


2
Contents
Introduction...............................................................................................................................................3
Methods......................................................................................................................................................3
Data Collection Procedure....................................................................................................................3
Research Design.....................................................................................................................................4
Hypotheses.............................................................................................................................................5
Data Analysis Results................................................................................................................................5
Discussion...................................................................................................................................................9
Conclusion................................................................................................................................................10
References................................................................................................................................................12

3
Do caffeine consumption, alcohol consumption, smoking amount, anxiety level, depression
level, weight and fatigue influence sleepiness level?
Introduction
Quality sleep is essential for overall individual well-being and productivity, but it can be
influenced by a variety of adaptable habits, ways of life, and mental health conditions. One of the
lifestyle factors that can affect the sleep cycle is alcohol consumption; it causes drowsiness and
interferes with the rapid eye movement stage (Koob & Colrain, 2020). This interference
contributes to fragmented sleep and elevated daytime sleepiness. Another common lifestyle
factor is caffeine, which can suppress sleepiness and subsequently reduce the quality of sleep as
a result of its stimulating impacts (Weibel et al. 2021). Also, nicotine from smoking has a
stimulating effect which interferes with sleep by contributing to frequent awakenings. Moreover,
depression and anxiety, which are significant mental health conditions, can lead to hyperarousal,
especially insomnia, which affects sleep quality (Freeman et al. 2020). Weight can also affect
sleep quality. Excessive weight is a risk factor for sleep apnea, which disrupts sleep quality
(Salzano et al. 2021). Also, physical exertion fatigue can affect sleepiness as the body seeks to
replenish its energy reserves (Kayser et al. 2022). Overall, this paper examines the influence of
these diverse factors based on the survey data collected from various individuals. The paper aims
to relate the result of this analysis to results found by scholars.
Methods
Data Collection Procedure
The study comprised a sample size of 209 participants. The participants were selected via
a voluntary response survey. They were adults aged 18 years and above and involved a diverse

4
range of demographics, including socioeconomic status, gender, age, and health backgrounds.
Certainly, the participants provided informed consent prior to conducting the research, thus
ensuring the ethical principle of autonomy was upheld. The criterion for inclusion in the survey
was based on the capability to comprehend and complete the survey independently.
Data collection was performed using a structured survey. <The survey was distributed
online and in paper format to elevate participation and accessibility rates. The survey was
structured to collect comprehensive data on lifestyle aspects and their potential effect on
sleepiness levels. The survey included straightforward questions with standardized response
options. It entailed various sections like weight, smoke, alcohol, caffeine, anxiety, depression,
fatigue and sleep. Indeed, each section targeted a specific variable under study. In the weight
section, the participants reported their weight. In contrast, in the smoke section, the participants
reported their smoking behavior, which was examined by the number of packets of cigarettes
smoked daily. The anxiety section reported anxiety levels based on a scale of 0 to 15. In the
depress section, the depression levels of the study participants were evaluated on a scale of 0 to
10. Within the fatigue section, the study participants indicated their fatigue levels on a scale of 0
to 10. While the level of sleepiness was evaluated based on a scale of 0 to 24.
Research Design
The research utilized a cross-section research design to examine how the dependent
variable related to predictor variables. The study predictor variables comprise caffeine
consumption, alcohol consumption, smoking amount, anxiety level, depression level, weight and
fatigue. The response variable is sleepiness level. Caffeine is a stimulant substance that elevates
the nervous system and brain activity. It is mainly found in tea and coffee. At the same time,
alcohol is a fermented or distilled liquid made up of ethanol. Smoke is a substance that is exhaled

5
or inhaled by sucking lit tobacco cigarettes.< Additionally, anxiety is the feeling of nervousness.
The level of anxiety is based on the severity of the associated symptoms. In contrast, depression
means low mood for an extended period. The depression level involves the severity of depressive
symptoms by the PHQ-9 scale. Fatigue involves the frequency and intensity of fatigue
symptoms, as reported by the participants. Sleepiness is a feeling of wanting to sleep. The
sleepiness level entails the level of sleepiness measured by the ESS.
Hypotheses
Null Hypothesis
It postulates that there is no association between response and predictor variables. The
independent variables, such as caffeine consumption, alcohol consumption, anxiety level,
depression level, smoking amount, fatigue, and weight, do not significantly influence the level of
sleepiness.
Alternative hypothesis
It states that there is a relationship between the predictor and response variable. At least one of
the response variables, caffeine consumption, alcohol consumption, anxiety level, depression
level, smoking amount, fatigue, and weight, significantly influence the level of sleepiness.
Data Analysis Results
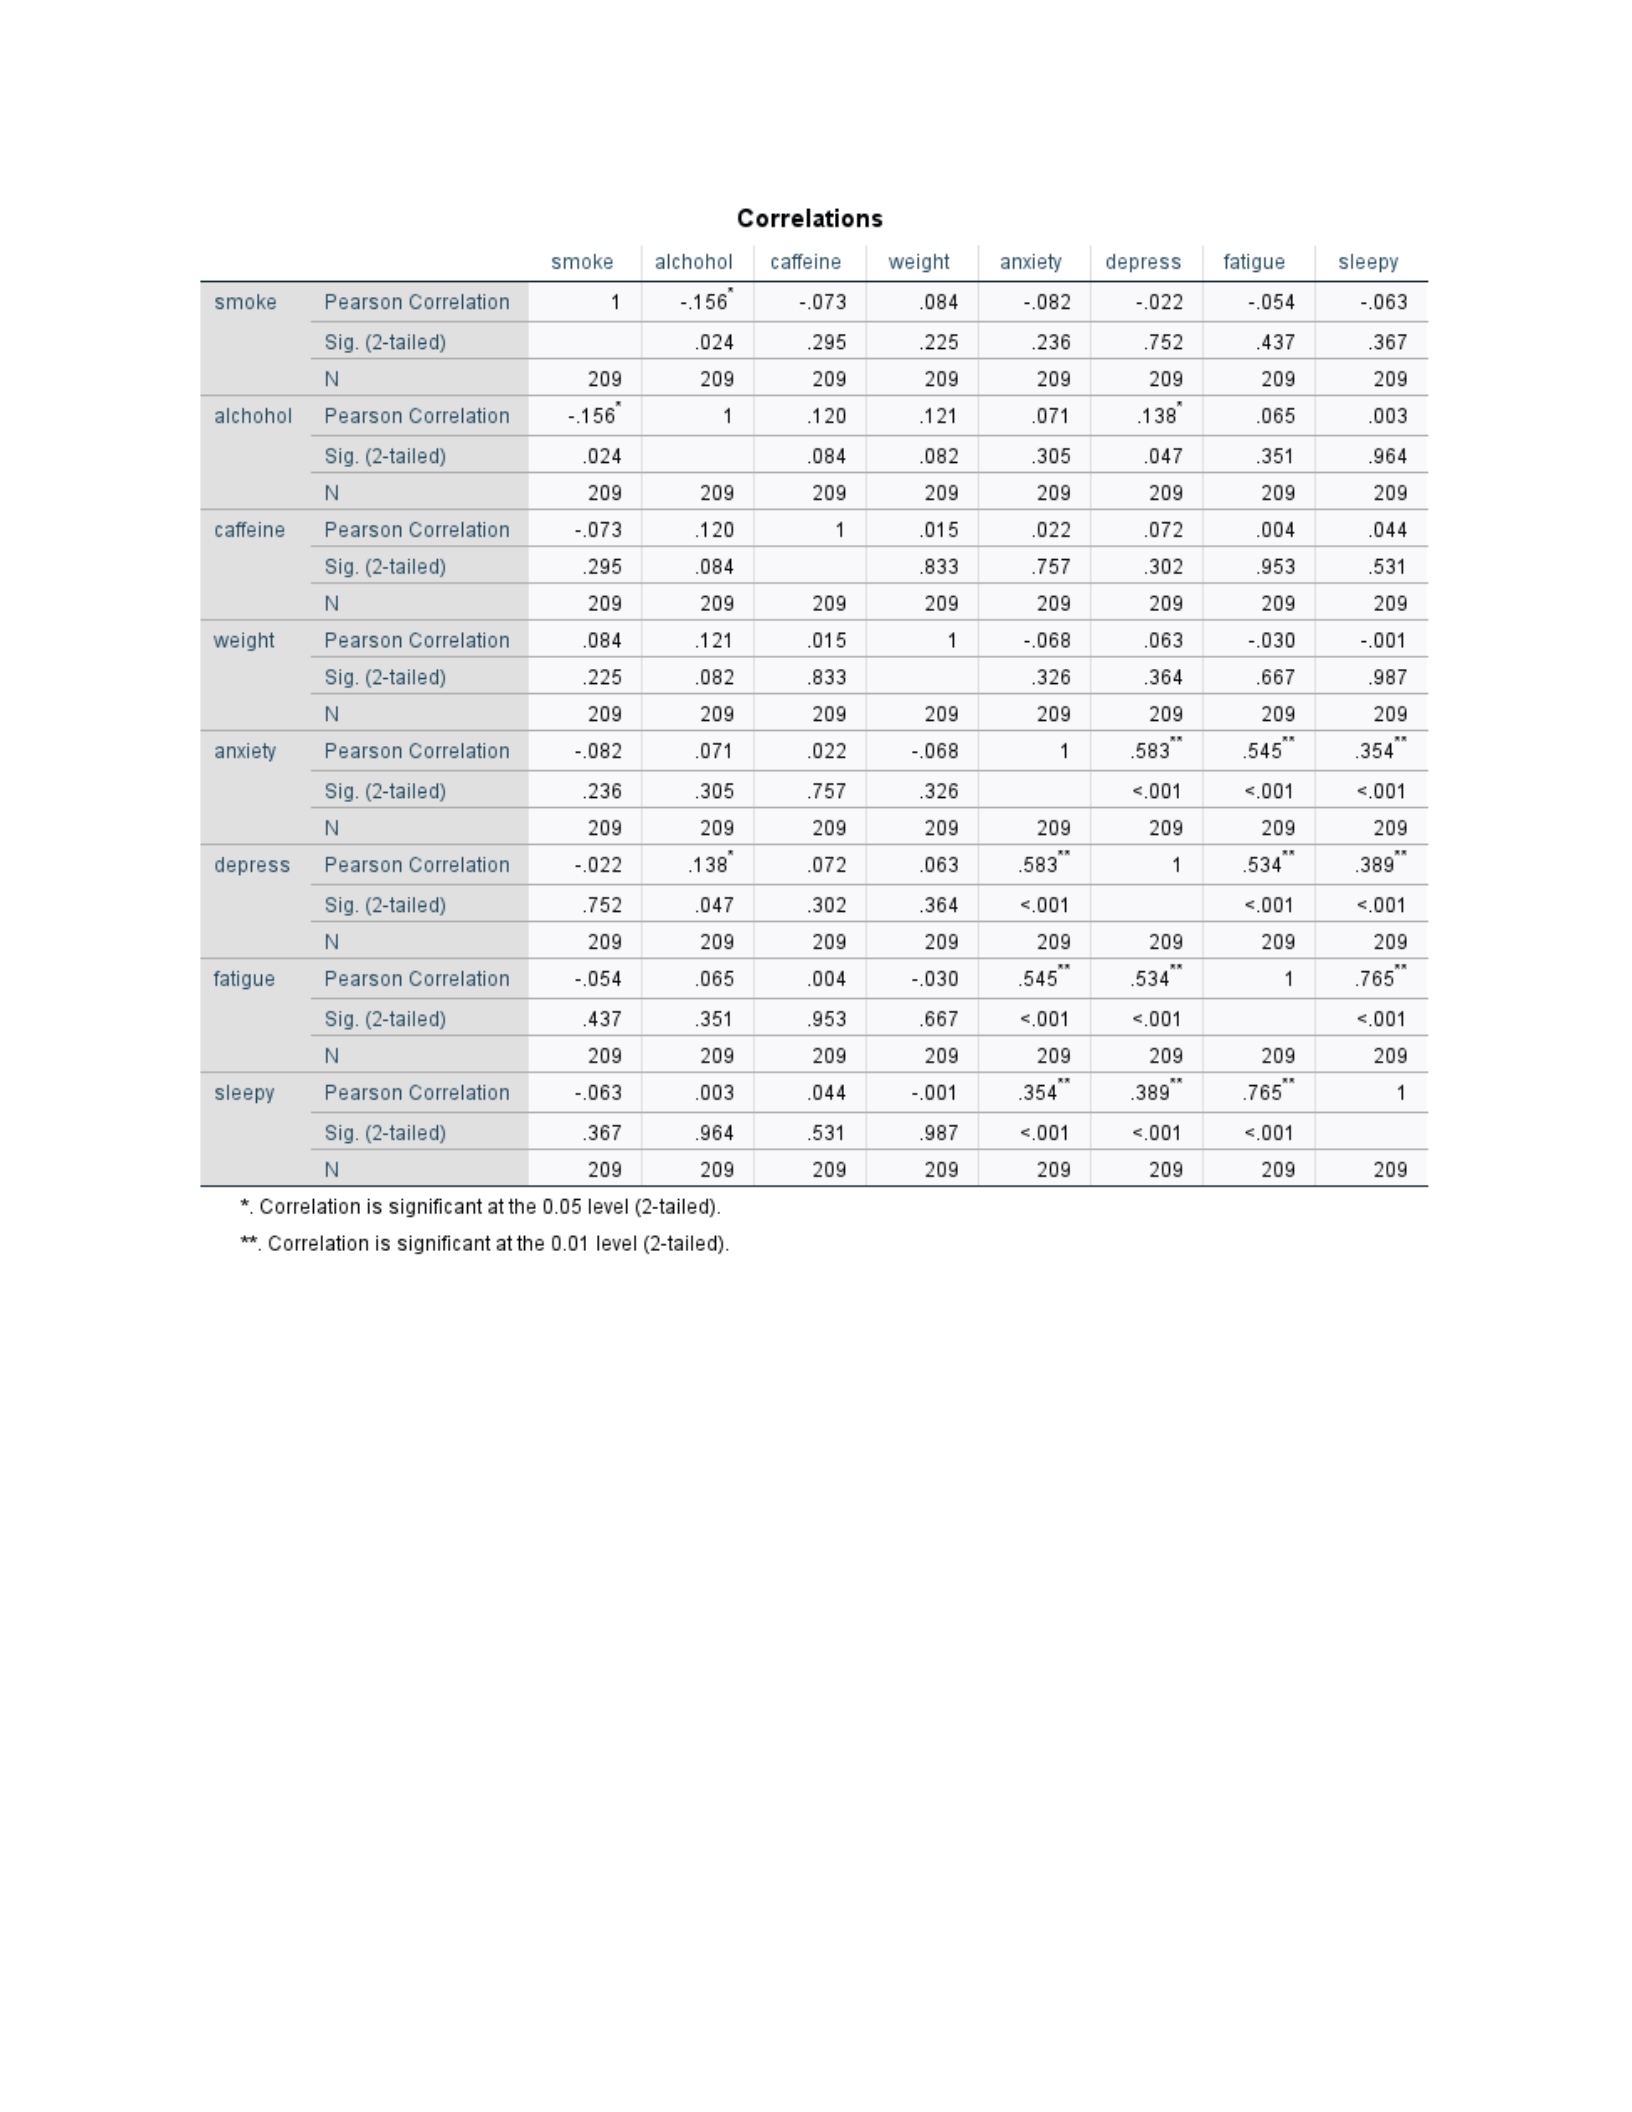
Firstly, a bivariate Pearson correlation analysis was conducted to evaluate the
relationships among all the variables collected to determine whether a statistically significant
linear relationship exists between two continuous variables.
6
Table 1: Bivariate Correlation Model
Indeed, based on the correlation table 1 above, sleepiness is positively correlated with
anxiety level (r = 0.354, p < 0.001), depression level (r = 0.389, p < 0.001) and fatigue level (r =
0.765, p < 0.001). While fatigue level is significantly associated with anxiety level (r = 0.545, p
< 0.001) and depression level (r = 0.534, p < 0.001). Caffeine consumption and weight do not
indicate substantial associations with any other factor. However, smoking does not significantly
7
correlate with other variables, except for its relationship with alcohol consumption (r = -0.156, p
= 0.024).
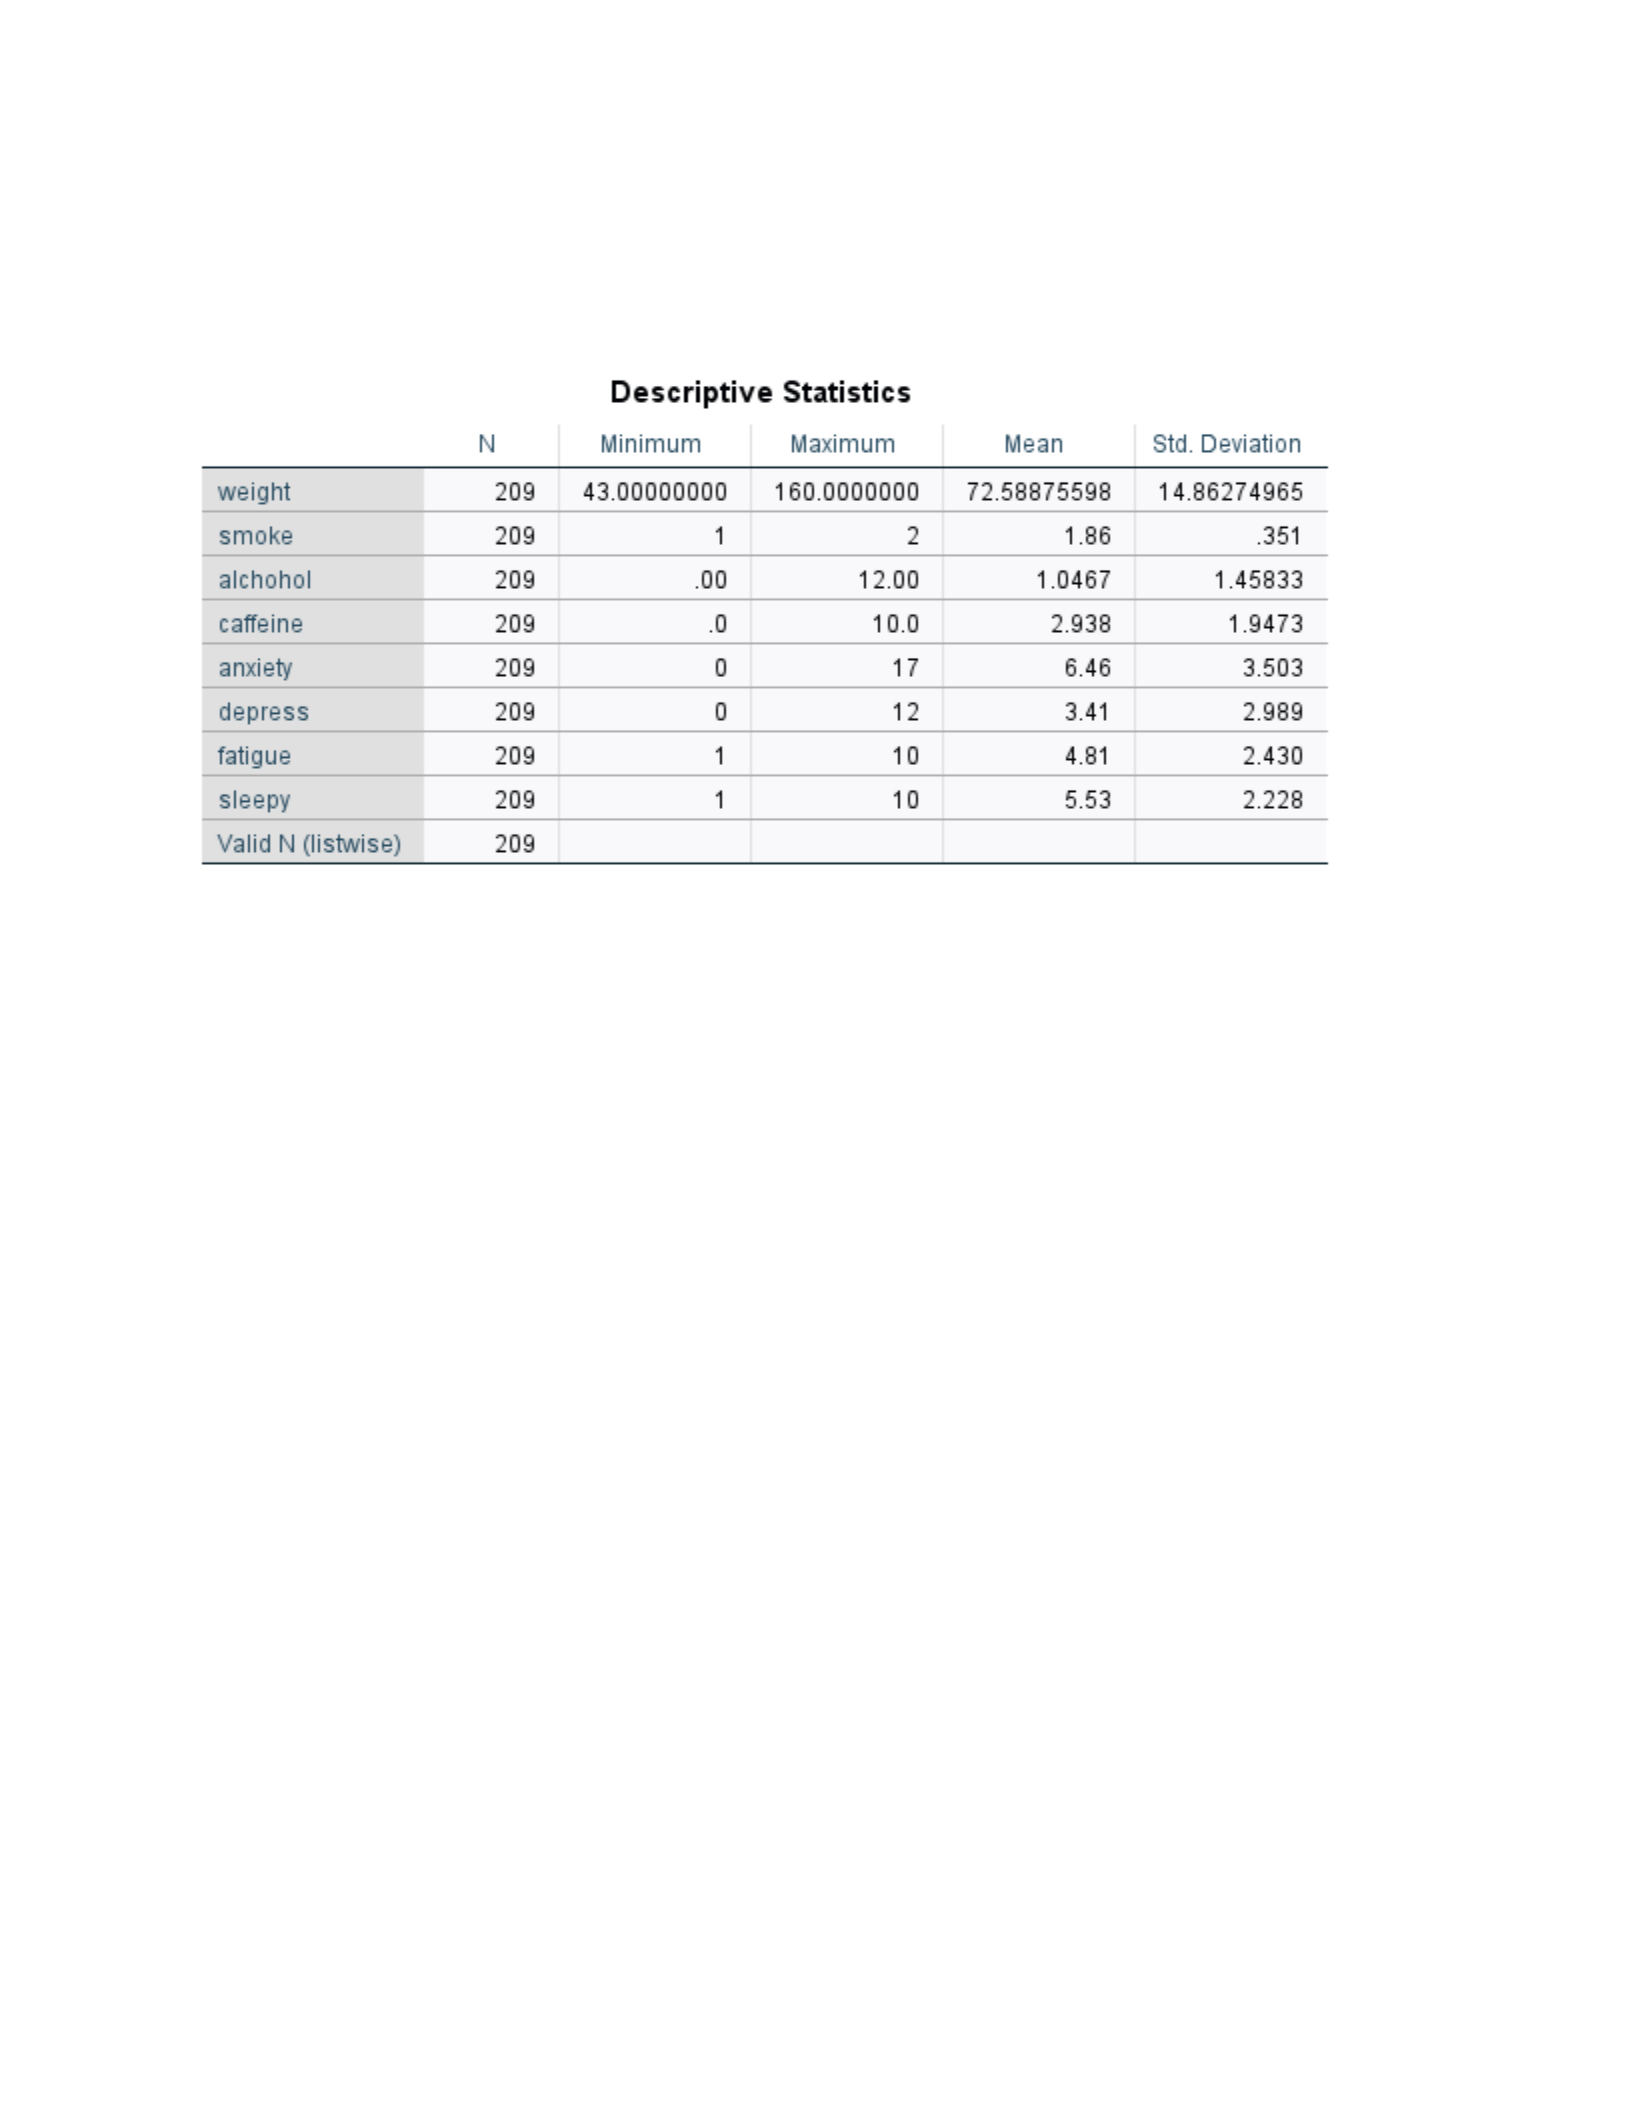
Table 2: Descriptive statistics
8
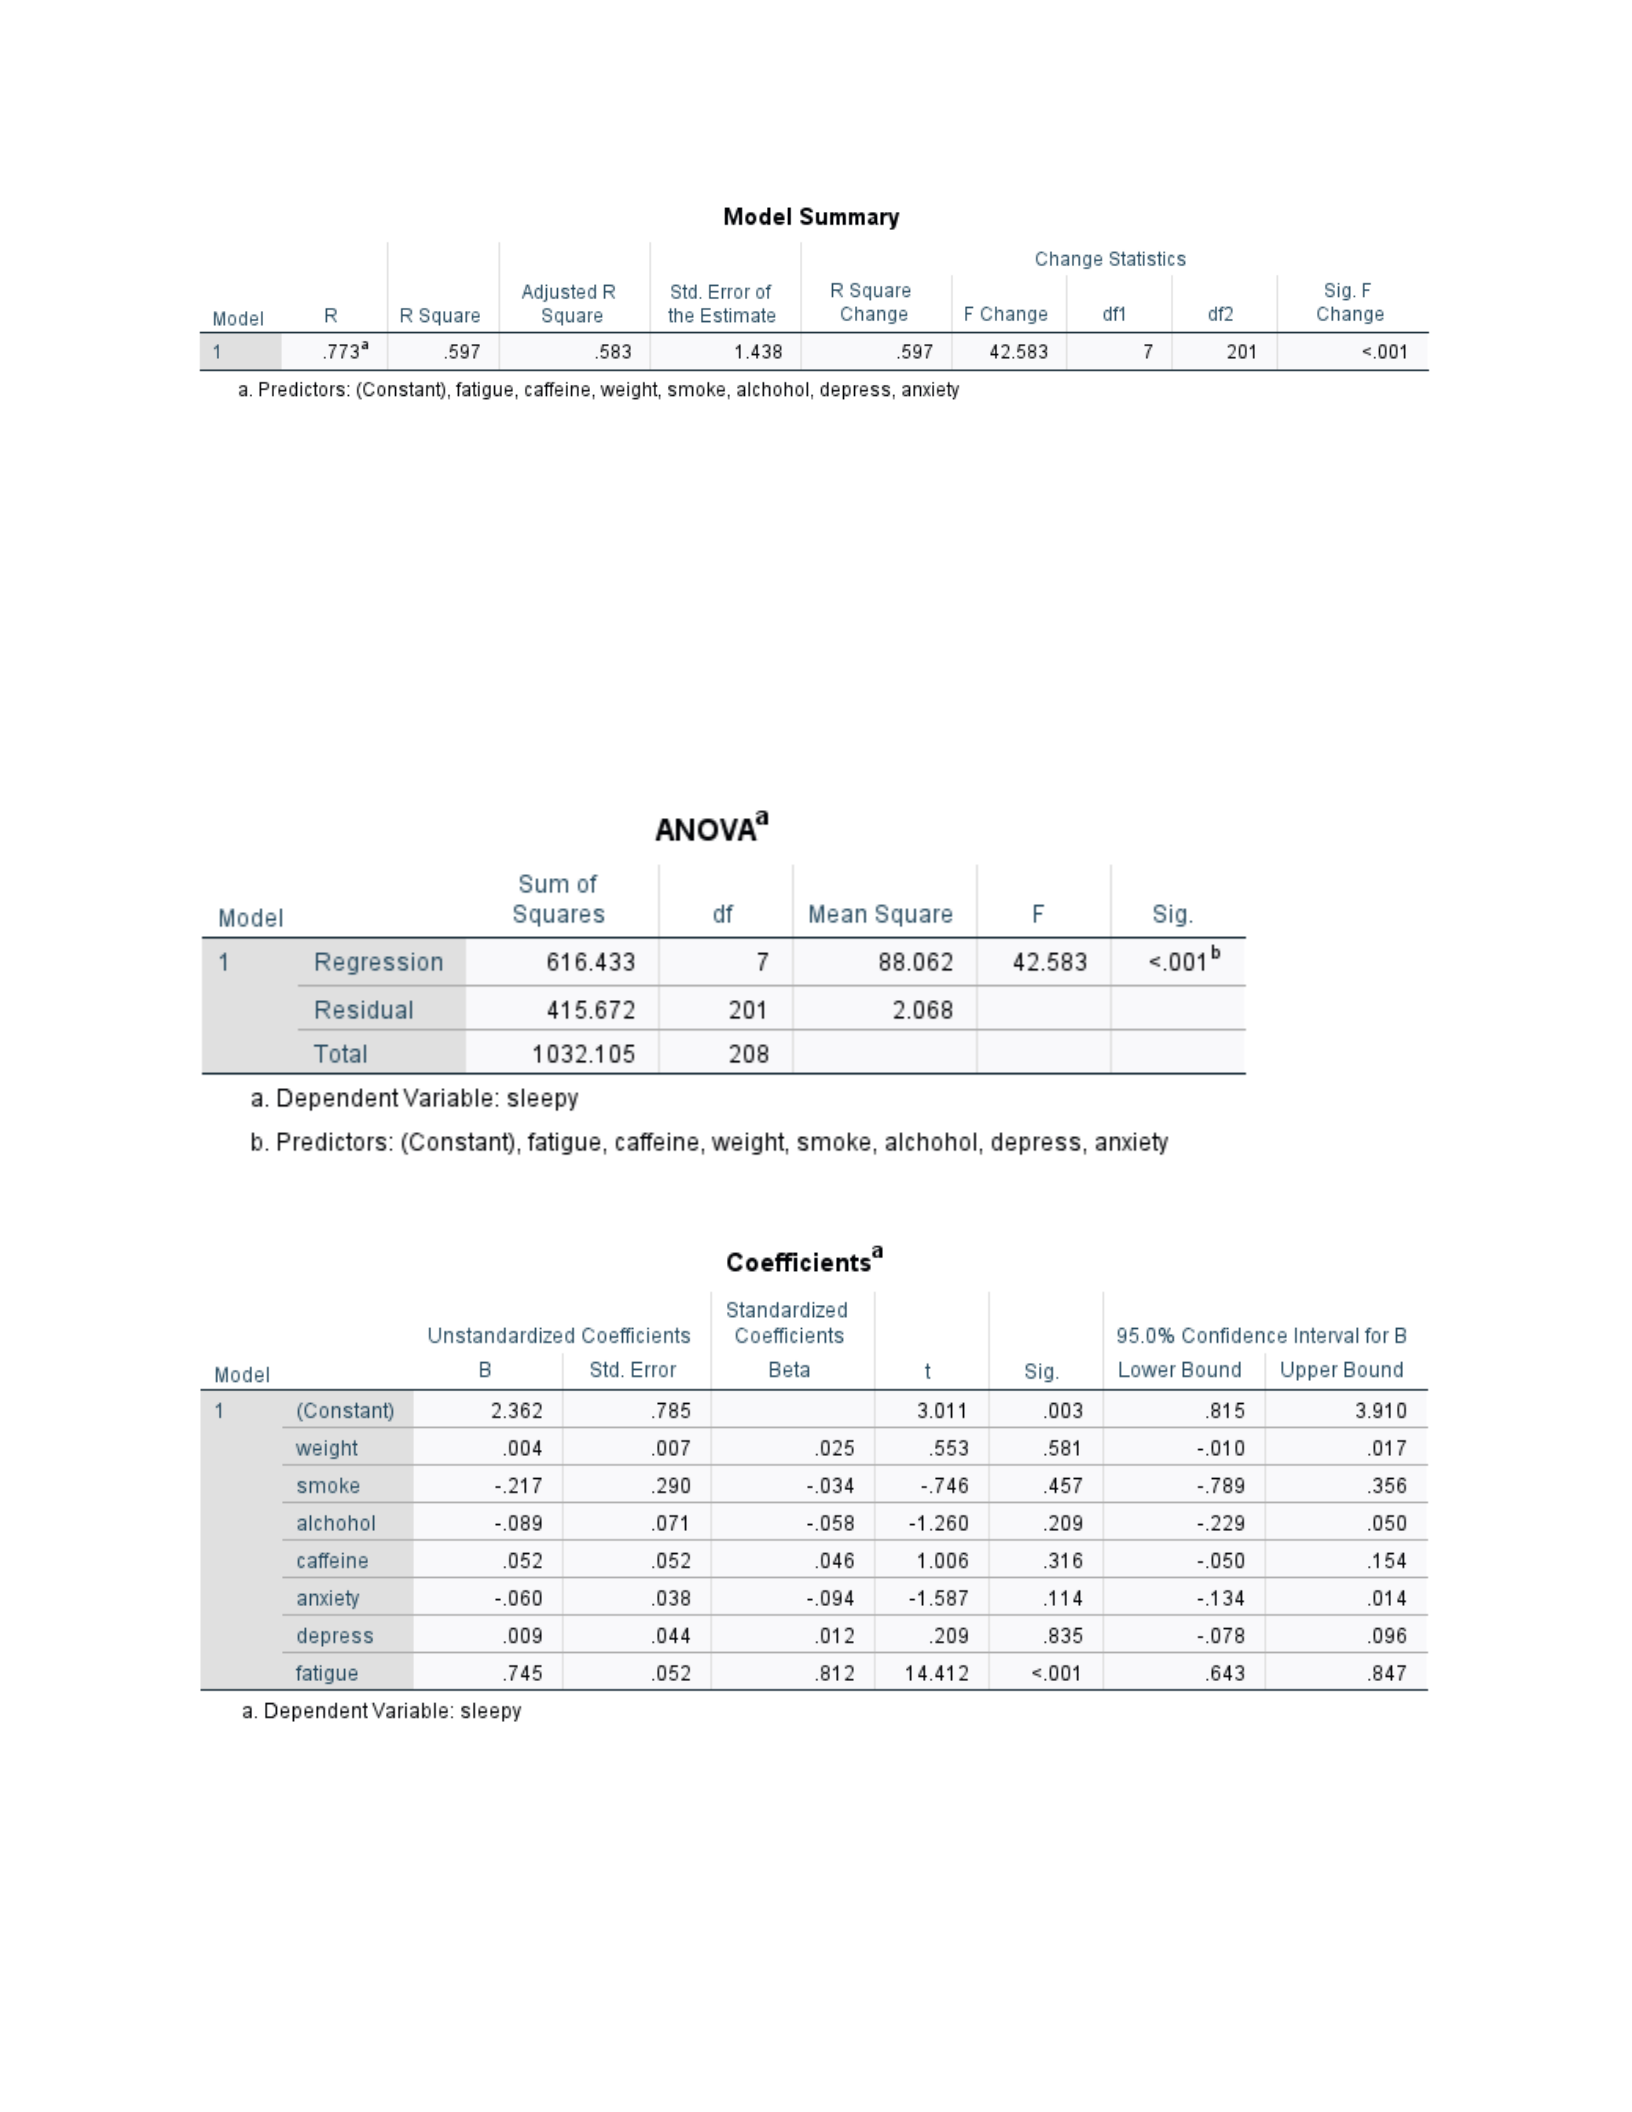
Table 3-4-5: Multiple Regression Model

9
Considering a bivariate relationship between two variables has been examined, multiple
regression analysis assisted in assessing the combined effect of multiple dependent variables:
caffeine consumption, alcohol consumption, anxiety level, depression level, smoking amount,
fatigue and weight on dependent variable level of sleepiness. The correlation coefficient (0.773)
demonstrates a robust correlation between the listed predictor variables and the dependent
variable. R-Square value demonstrates that the model accounts for 59.7% of variance in the
dependent variable. The F-value of 42.583 shows that the model is statistically valid (p < 0.001);
this demonstrates that the independent variables have a combined effect on the response variable.
Testing hypothesis
Therefore, with the understanding that the predictor variables have a combined effect on
the dependent variable, interpretation of coefficients is crucial to test hypotheses. Certainly,
based on the study data, the fatigue variable has the most significant standardized coefficient
(Beta 0.812), demonstrating that higher fatigue levels are related to increased sleepiness. The
fatigue variable has an unstandardized coefficient of 0.745, demonstrating that for every unit rise
in fatigue, the sleepiness score elevates by 0.745 units, while other factors remain steady. The p-
value is less than 0.001, demonstrating that the effect is statistically evident. <The p-value of
weight (0.581) is higher than 0.05, illustrating that it does not significantly predict sleepiness
based on this study data. Smoke, alcohol, caffeine and anxiety have p-values of 0.457, 0.209,
0.316, and 0.114, respectively, showing they do not significantly predict sleepiness. <The model
is statistically significant, explaining about 59.7% of the variance in sleepiness. Thus, the null
hypothesis is rejected, demonstrating that at least one independent variable (fatigue) significantly
affects sleepiness.

10
Discussion
This study focuses on the influence of various factors, including caffeine consumption,
alcohol consumption, anxiety level, depression level, smoking amount, fatigue and weight,
which significantly influence the level of sleepiness, indicating that fatigue has a significant
influence on the level of sleepiness. Surprisingly, other factors, caffeine consumption, alcohol
consumption, anxiety level, depression level, smoking amount, and weight significantly
influence do not have a significant influence on the level of sleepiness based on the study data.
Åkerstedt et al. (2023) study indicates that poor sleep is associated with fatigue; this shows a
positive correlation elaborated in this present study. The p-value of the fatigue variable as an
independent variable was less than 0.05, indicating fatigue significantly influences sleepiness.
The correlation between sleepiness and alcohol consumption in this research concurs with results
demonstrated by Vinson et al. (2010), which found that the level of sleep quality is not
influenced by alcohol consumption. In this study, alcohol consumption did not affect sleepiness
because of the likelihood of low rates of alcohol consumption.
Ebrahim et al. (2013) found that rapid eye movement (REM) sleep was reduced and
increased during the first half and second half of the sleep cycle respectively; in this research,
healthy persons were instructed to drink alcohol. Although this study does not significantly
explain the effect of alcohol on sleepiness, Peppard et al. (2007) found that consumption of
alcohol elevates sleep apnea. Thus, alcohol prevents entry into deep sleep since it puts
individuals more at risk of sleep disturbance, according to Peppard et al. (2007).
Moreover, according to Oh et al. (2019), anxiety and depression disrupt sleepiness or the
general quality of sleep. Likewise, in this research, there is a substantial association between
depression or anxiety and worsening in sleepiness. Additionally, O’callaghan et al. (2018) show

11
that caffeine disrupts sleep by blocking adenosine, which is a natural sleep-inducer, and this
shortens the sleep duration. However, the findings of this research indicate that there is no
positive correlation between consumption of caffeine and the level of sleepiness. The study
shows that being overweight can influence the level of sleepiness. Obesity can contribute to
sleep disturbances. Mainly, obstructive sleep apnea is the most common sleep disorder
associated with obesity or overweight. However, this present study shows that there is no
correlation between weight and the level of sleepiness. Notably, key limitation of this research is
that the finding might not represent the general population, as the data was not collected from
diverse groups.
Conclusion
This research explores how various lifestyle factors affect sleepiness. The results
indicated that fatigue has a positive correlation with sleepiness levels. Individuals with more
significant levels of fatigue are more likely to experience sleepiness. Surprisingly, various
independent factors like alcohol and caffeine consumption, weight, and smoking, which were
believed to influence sleep within the studied range, did not have a positive correlation with
sleepiness in this data sample. Certainly, the findings of this research illustrate the significance of
addressing fatigue as a probable cause of daytime sleepiness. Future research should investigate
the underlying mechanism associated with fatigue and sleepiness in more detail and include
participants from a broad geographic region and diverse backgrounds. This study has practical
implications. By identifying fatigue as a critical attribute of sleepiness, employers and healthcare
workers can better address factors that might lead to fatigue and structure evidence-based
interventions.

12
2. In any research, why is describing the variability important?
Describing variability is research is important to understand data distribution. Variability enables
researchers to compare data within different groups with or across researches to evaluate consistency.
Variability assist in assessing uncertainty in study findings.
4. What is the difference between what a measure of central tendency tells us and what a measure of
variability tells us?
Measure of central tendency focuses on the center of the data, and tells where most of the data points
tend to cluster around. The measures of central tendency include, mode, media and median. While
measure of variability fosters on the spread of data and tells how data points are scatters around the
central values.
6. (a) What is the mathematical definition of the variance? (b) Mathematically, how is a sample's
variance related to its standard deviation and vice versa?

13
The variance (σ^2) of a dataset represents the average squared deviation of each data point from
the mean (μ). It measures how spread out the data is from the average value.
Here's the formula for variance:
σ^2 = (Σ (x_i - μ)^2) / N
where:
σ^2 - Population variance (variance of the entire population)
Σ - Summation symbol (summing over all data points)
x_i - Individual data point in the set
μ - Mean of the data set
N - Total number of data points in the set (population size)
Relationship between Variance and Standard Deviation:
The standard deviation (σ) is the square root of the variance (σ^2). It expresses the spread of the
data in the same units as the original data points, making it easier to interpret the magnitude of
variation.
Here's the mathematical relationship:
σ = √σ^2
8. Why is the mean a less accurate description of the distribution if the variability is large than if it is
small?
The mean is a less accurate description of the distribution if the variability is large because the
mean only considers the average value and doesn't account for how spread out the data is. Here's
why:
The Mean Represents a Single Point: The mean simply tells you the central location of
the data by averaging all the values. However, it doesn't tell you anything about how
spread out those values are from the average.
Large Variability Means Data Points Scattered: When you have high variability, the
data points are scattered widely around the mean. There could be a significant number of
values far above and below the mean, making the mean less representative of the
majority of the data.
10. (a) What do S, s, and have in common? (b) How do they differ in their use?
(a) Commonalities:

14
All three symbols (S, s, and σ) represent measures of spread or variability within a
dataset. They indicate how far individual values deviate from the central tendency
(usually the mean).
They are all expressed in squared units of the data (e.g., if data is in meters,
variance/standard deviation will be in square meters).
(b) Differences in Use:
Symbol Description Use Case
σ² (sigma
squared)
Population
Variance
Represents the variability of the entire population from which
a sample is drawn (assuming the population is finite). We
rarely have access to the entire population, so σ² is often
estimated.
s² (s squared) Sample Variance
Represents the variability within a sample, used to estimate
the population variance when we don't have data for the entire
population.
σ (sigma)
Population
Standard
Deviation
Square root of the population variance (σ²), expresses spread
in the same units as the original data.
s (sample
standard
deviation)
Sample Standard
Deviation
Square root of the sample variance (s²), also expresses spread
in the original units, but used to estimate the population
standard deviation.
12. Why are your estimates of the population variance and standard deviation always larger than
the
Estimates of population variance and standard deviation based on a sample tend to be larger than
the corresponding values that describe the actual sample. There are two main reasons for this:
1. Sampling Error: When you only use a sample of the population to estimate population
parameters like variance and standard deviation, you introduce sampling error. This error
arises because the specific sample you draw might not perfectly represent the variability
of the entire population. For example, imagine a population of exam scores with a wide
range. A small sample might contain mostly average scores by chance, missing the high
and low outliers that contribute to the population's spread.
2. Divisor Adjustment for Sample Variance: To partially compensate for sampling error,
we use a different divisor when calculating sample variance (s²) compared to population
variance (σ²). The population variance uses the total population size (N) as the divisor,
while the sample variance uses (N-1). This adjustment acknowledges that the sample
doesn't perfectly capture all the population's variability, so we use a slightly smaller
divisor to avoid underestimating the spread even further.

15
14. If you could test the entire population in question 13, what would you expect each of the
following to be? (a) The typical, most common score; (b) the variance; (c) the standard
deviation; (d) the two scores between which 68% of the scores lie.
(a) The typical, most common score:
Answer: This is the mode, the score that appears most frequently. For the given scores,
the mode is 4.
(b) The variance:
Answer: If we test the entire population, the variance remains the same as calculated
from the sample, which is approximately 6.49.
(c) The standard deviation:
Answer: The standard deviation would remain the same, approximately 2.55.
(d) The two scores between which 68% of the scores lie:
Answer: The scores between which 68% of the scores lie are approximately
1.551.551.55 to 6.656.656.65, as calculated earlier.
16. From his statistics grades, Demetrius has a X = 60 and Sx 20. Andrew has X = 60 and Sx =
8. (a) Who is the more inconsistent student and why? (b) Who is more accurately described as a
60 stu- dent and why? (c) For which student can you more accurately predict the next test score
and why? (d) Who is more likely to do either extremely well or extremely poorly on the next
exam and why?
(a) Who is the more inconsistent student and why?
Answer: Demetrius is the more inconsistent student because his standard deviation (20)
is higher than Andrew's (8), indicating more variability in his scores.
(b) Who is more accurately described as a 60 student and why?
Answer: Andrew is more accurately described as a 60 student because his scores have
less variability (standard deviation of 8) compared to Demetrius's scores (standard
deviation of 20).
(c) For which student can you more accurately predict the next test score and why?

16
Answer: Andrew's next test score can be predicted more accurately because his scores
are less variable (standard deviation of 8), making his future performance more
consistent.
(d) Who is more likely to do either extremely well or extremely poorly on the next exam
and why?
Answer: Demetrius is more likely to do either extremely well or extremely poorly on the
next exam because his scores are more variable (standard deviation of 20), indicating a
wider range of possible outcomes.
References
Åkerstedt, T., Schwarz, J., Theorell-Haglöw, J., & Lindberg, E. (2023). What do women mean
by poor sleep? A large population-based sample with polysomnographical indicators,
inflammation, fatigue, depression, and anxiety.<Sleep Medicine,<109, 219-225.
Ebrahim, I. O., Shapiro, C. M., Williams, A. J., & Fenwick, P. B. (2013). Alcohol and sleep I:
effects on normal sleep.<Alcoholism: Clinical and Experimental Research,<37(4), 539-
549.

17
Freeman, D., Sheaves, B., Waite, F., Harvey, A. G., & Harrison, P. J. (2020). Sleep disturbance
and psychiatric disorders.<The Lancet Psychiatry,<7(7), 628-637.
Kayser, K. C., Puig, V. A., & Estepp, J. R. (2022). Predicting and mitigating fatigue effects due
to sleep deprivation: A review.<Frontiers in Neuroscience,<16, 930280.
Koob, G. F., & Colrain, I. M. (2020). Alcohol use disorder and sleep disturbances: a feed-
forward allostatic framework.<Neuropsychopharmacology,<45(1), 141-165.
O’callaghan, F., Muurlink, O., & Reid, N. (2018). Effects of caffeine on sleep quality and
daytime functioning.<Risk management and healthcare policy, 263-271.
Oh, C. M., Kim, H. Y., Na, H. K., Cho, K. H., & Chu, M. K. (2019). The effect of anxiety and
depression on sleep quality of individuals with high risk for insomnia: a population-based
study.<Frontiers in neurology,<10, 849.
Peppard, P. E., Austin, D., & Brown, R. L. (2007). Association of alcohol consumption and sleep
disordered breathing in men and women.<Journal of Clinical Sleep Medicine,<3(3), 265-
270.
Salzano, G., Maglitto, F., Bisogno, A., Vaira, L. A., De Riu, G., Cavaliere, M., ... & Salzano, F.
A. (2021). Obstructive sleep apnoea/hypopnoea syndrome: relationship with obesity and
management in obese patients.<Acta Otorhinolaryngologica Italica,<41(2), 120.
Vinson, D. C., Manning, B. K., Galliher, J. M., Dickinson, L. M., Pace, W. D., & Turner, B. J.
(2010). Alcohol and sleep problems in primary care patients: a report from the AAFP
National Research Network.<The Annals of Family Medicine,<8(6), 484-492.

18
Weibel, J., Lin, Y. S., Landolt, H. P., Berthomier, C., Brandewinder, M., Kistler, J., ... &
Reichert, C. F. (2021). Regular caffeine intake delays REM sleep promotion and
attenuates sleep quality in healthy men.<Journal of biological rhythms,<36(4), 384-394.

