


1
Chapter 1: Introduction to the Study
Marriage and family therapists are uncomfortable discussing topics of a sexual
nature (Cupit, 2010; Harris & Hays, 2008). Researchers have found that this lack of
comfort has persisted (Dermer & Bachenberg, 2015). Beginning therapists are
particularly prone to avoid sexual topics with their clients (Timm, 2009). Comfort
impacts competency; knowledge alone is not sufficient (Dermer & Bachenberg, 2015). It
is important to be both comfortable and knowledgeable as a therapist (Voss, 2015). The
World Health Organization (2006) affirmed sexual health as a human right, and
according to Dermer and Bachenberg (2015), therapists should affirm sexual health to
their clients. However, adequate training to improve therapist comfort levels in sexual
topics has not increased during the past 40 years (Dermer & Bachenberg, 2015).
Attitudes and knowledge have an impact on how therapists practice therapy and how they
implement interventions (Dermer & Bachenberg, 2015). Understanding therapists’
attitudes toward sexuality will provide a better understanding of how attitudes impact the
comfort level of the therapist when engaging the client on sexual topics (Dermer &
Bachenberg, 2015; Russell, 2012).
In Chapter 1, I present an overview of this study, including a description of the
social problem, gaps in the literature, and hypotheses. I introduce Bowen’s (1976) theory,
which provided the framework for the study. Finally, I define the terms and variables,
present the research design, and discuss the limitations, delimitations, assumptions, and
significance of the study.

2
Background
Harris and Hays’s (2008) research on marriage and family therapists’ willingness
to engage in discussions of sexuality with their clients was the seminal work in this area
and the only peer-reviewed journal article that addressed this variable within the
Bowenian theoretical framework. Harris and Hays published their first study addressing
marriage and family therapists’ attitudes toward lesbian, gay, bisexual, and transgender
(LGBT) individuals in 2012. There has been some research into the link between licensed
clinical marriage and family therapists’ (LCMFT) attitudes and comfort, and between
LCMFTs’ attitudes and practice (Anderson, 2002; Giami & Pacey, 2006; Juergens, 2006;
Weerakoon & Stiernborg, 1996; Yelton & Delfin, 2015). There have been studies on the
link between LCMFT knowledge, comfort, and attitudes toward sexuality (West et al.,
2012). There have also been studies addressing how LCMFT comfort and knowledge
impact willingness to discuss sexuality (Hanzlik & Gaubatz, 2012; Harris & Hays, 2008).
Only two studies addressed all four variables concerning how knowledge and
attitudes about human sexuality impact comfort and willingness to engage with clients
about their sexuality, but neither included participants from the marriage and family
therapy community; instead, the authors surveyed counselors (Cupit, 2010; Juergens,
2006). Sexuality is important to the individual and is recognized not only for its
importance but as a human right by the World Health Organization (2006). Therapists
who do not address sexuality with their clients can cause harm both to themselves and the
client (Cupit, 2010; LoFrisco, 2013; Ridley, 2006). Therapists are still “not comfortable
discussing sexual issues with their clients” (Cupit, 2010, p. 9), and this is leading to harm

3
(Dermer & Bachenberg, 2015). There has not been a study addressing all of the variables
as applied to marriage and family therapists. I intended for this study to fill the gap in the
literature to increase the understanding of how personal attitudes about human sexuality
factor into marriage and family therapists’ willingness to discuss sexual topics with their
clients. Findings may improve therapists’ abilities to address this issue by reducing their
anxiety and reducing the chance of harm to clients.
Problem Statement
The research problem was that marriage and family therapists are not comfortable
discussing sexual issues with clients to the point of not being willing to broach the topic
(Cupit, 2010; Dermer & Bachenberg, 2015; Harris & Hays, 2008; LoFrisco, 2013; Timm,
2009). Therapists may cause significant damage by not proactively addressing the issue
of sexual health or by dismissing it when brought up by the client (Cupit, 2010; Harris &
Hays, 2008; Juergens, Smedema, & Berven, 2009; LoFrisco, 2013; Papaharitou et al.,
2008; Timm, 2009). Many therapists fail to assist their clients in dealing with these issues
(Harris & Hays, 2008; Juergens et al., 2009; Papaharitou et al., 2008). Based on a
literature search of many databases, I found only one peer-reviewed journal article that
addressed marriage and family therapists discussing sexual issues with clients in which
the researchers found a link between knowledge, comfort, and willingness to engage
(Harris & Hays, 2008). I found only two peer-reviewed journal articles addressing the
link between attitudes and comfort (Hanzlik & Gaubatz, 2012; Russell, 2012).
Furthermore, I found only one peer-reviewed journal article addressing the variable of
willingness to engage clients in sexual discussions with a marriage and family therapist

4
(Harris & Hays, 2008). If therapists do not help clients to feel comfortable talking about
their sex life because they will not broach the topic of sexuality, then they should address
this problem (Harris & Hays, 2008). Building upon the previous research by examining
the variable of therapists’ attitudes compared with the other three variables of knowledge,
comfort, and willingness was needed to increase the knowledge base in the field (Cupit,
2010; Dermer & Bachenberg, 2015; Harris & Hays, 2008; LoFrisco, 2013; Miller &
Byers, 2012; Russell, 2012).
Purpose
In this quantitative study, I used Bowenian theory to examine the relationship
between therapists’ attitudes, knowledge, comfort, and willingness to engage clients in a
discussion of their sexuality (see Harris & Hays, 2008; Kerr & Bowen, 1988; Schnarch,
1998). The independent variables were (a) attitudes, (b) knowledge, (c) training, (d)
supervision experience, (e) clinical experience, (f) sex, (g) age, (h) strength of religion, (i)
sexual orientation, (j) practice experience, (k) practice setting, (l) graduate specialization,
and (m) relationship status; the dependent variables were (a) comfort and (b) willingness
to engage.
Research Questions and Hypotheses
The following research questions (RQs) and hypotheses were used to guide the
study:
RQ1: What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s willingness to discuss sexual topics
with clients?

5
H01: There is no statistically significant relationship between attitudes,
knowledge, training, supervision experience, and clinical experience and a therapist’s
willingness to discuss sexual topics with clients.
Ha1: There is a statistically significant relationship between attitudes, knowledge,
training, supervision experience, and clinical experience and a therapist’s willingness to
discuss sexual topics with clients.
RQ2: What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s comfort discussing sexual topics
with clients?
H02: There is no statistically significant relationship between attitudes,
knowledge, training, supervision experience, and clinical experience and a therapist’s
comfort discussing sexual topics with clients.
Ha2: There is a statistically significant relationship between attitudes, knowledge,
training, supervision experience, and clinical experience and a therapist’s comfort
discussing sexual topics with clients.
RQ3: What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s comfort level with sexuality?
H03: There is no statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort level with sexuality.

6
Ha3: There is a statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort level with sexuality.
RQ4: What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s willingness to discuss sexual
topics with clients?
H04: There is no statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to discuss sexual topics with clients.
Ha4: There is a statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to discuss sexual topics with clients.
RQ5: What is the relationship between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of
the sexual comfort of a therapist?
H05: There is no statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of the sexual comfort of a therapist.
Ha5: There is a statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of

7
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of the sexual comfort of a therapist.
RQ6: What is the relationship between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of a
therapist’s willingness to discuss sexual topics?
H06: There is no statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to discuss sexual topics?
Ha6: There is a statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to discuss sexual topics.
Theoretical Base
The theoretical framework for this study was Bowenian theory (see Baer &
Murdock, 1995; Bowen, 1976; Harris & Hays, 2008; Kerr & Bowen, 1988; Schnarch,
1998). Bowen (1976) developed this theory as a practicing therapist while observing
families in both structured and unstructured settings. Bowen examined the ability of
therapists to remain emotionally present and nonreactionary while being able to express
their values and dispense assessments (Baer & Murdock, 1995). The major theoretical
constructs of Bowenian theory appropriate for this study were therapists’ anxiety and

8
reactivity (see Cupit, 2010; Harris & Hays, 2008). According to Bowenian theory, it is
difficult for therapists to be helpful to clients in the therapeutic relationship when the
therapists’ emotional reactions interfere with their awareness (Kerr & Bowen, 1988;
Schnarch, 1991). According to Harris and Hays (2008), “Bowen’s concepts of anxiety
and reactivity are helpful in conceptualizing why a therapist might not engage his or her
clients in a discussion of sexuality” (p. 241). Basing this study on Bowenian theory may
add to the understanding of how these variables fit into a system and impact therapists
and how they may or may not relate to each other in decreasing anxiety (see Baer &
Murdock, 1995; Harris & Hays, 2008). The goal of this study was to increase the
understanding of how therapists may decrease their anxiety so they can positively engage
the client in discussions of sexuality (Harris & Hays, 2008).
Nature of the Study
The nature of this study was quantitative. Previous studies had used quantitative
methods based on Bowenian theory. I used a correlational study design to examine
relationships among the variables.
Definitions
Attitudes (toward discussing sexuality with the client): Therapists’ attitudes in this
study were defined as therapists being aware of their biases, beliefs, and judgments and
not allowing them to negatively influence their view of their clients as individuals or the
subject matter broached by the client in the therapeutic relationship. A negative attitude
toward a client’s sexual orientation would constitute a barrier to the therapist’s

9
effectiveness. Through self-understanding, negative attitudes can be avoided (Cort,
Attenborough, & Watson, 2001; Masters & Johnson, 1970).
Comfort with sexual discussions: The therapist’s ability to (a) accept and respect
clients’ sexual practices, (b) have open discussions about clients’ sexuality, and (c)
communicate effectively regarding sexuality (Graham & Smith, 1984). Comfort with
discussing sexual issues is a broad concept involving “cognitive, affective, and
behavioral responses to sexuality” (Graham & Smith, 1984, p. 439). The ability to be
comfortable with sexual issues is “a developmental task influenced by the physiological,
psychological, sociological, spiritual or religious, educational, and sexual aspects of one’s
being.” (Graham & Smith, 1984, p. 440).
Sexual issues: Sexual issues and dysfunctions “are broadly defined as any sexual
concern a client may have and the psychological issues that accompany it” (LoFrisco,
2013, p. 17). Examples of common sexual issues include “sexual performance, sexual
dysfunctions, gender issues, sexual abuse, sexual disorders, sexual addiction, sexual
trauma, sexual shame and sexual intimacy issues” (LoFrisco, 2013, p. 17).
Sexual knowledge: “Sexual knowledge is defined as possession of correct
information regarding human sexuality, including a good understanding of the dynamics
and psychological effects of sexual dysfunctions, information about the sexual response
phases, and an awareness of what is considered to be normal or average” (LoFrisco,
2013, p. 17).

10
Willingness (to engage a client in a discussion about sexuality): The likelihood
that the therapist will proactively broach or discuss sexual issues with the client (Harris &
Hays, 2008).
Assumptions
I made several assumptions in this quantitative correlational study. I assumed that
therapists want to help their clients. I also assumed that therapists who filled out their
surveys were honest and that the information provided by them was accurate. I assumed
that the therapists who filled out the survey were representative of the larger population. I
assumed, as did Cupit (2010), that “the instruments that were used in this study are
reliable and valid and accurately measure sexual comfort [and therapists’] sexual
attitudes, sexual knowledge, training experience with sexual issues, supervision
experience addressing sexuality, and clinical experience with sexual issues” (p. 14). I
assumed that the participants volunteered willingly and that their answers did not reflect
any impairment or agenda or were given while under duress. Because the participants
answered questions anonymously, I assumed that the participants were licensed marriage
and family therapists and that they fully understood the informed consent packet and how
anonymity and confidentiality worked as it pertained to the survey. These assumptions
were necessary to meet the demands of social science research standards as laid out by
Creswell (2013).
Scope and Delimitations
I limited the study to licensed marriage and family therapists practicing in the
United States. The study focused on the quantitative gaps in the research regarding how

11
therapists’ knowledge and attitudes impact comfort and willingness to engage clients.
The study included an online survey made up of seven scales to assess these variables
and their potential correlations. Therapists answered questions regarding their knowledge
of sexual issues/sexuality, attitudes toward sexual issues/sexuality, training, education,
clinical experience, and supervision experience. Additionally, therapists answered
questions regarding their comfort while discussing sexual issues with clients and their
willingness to initiate the discussion with a client regarding sexual issues. I tested the
hypotheses using a quantitative correlational research design (see Bramante, 2015), and
research questions to determine whether there were any relationships between the
independent variables and dependent variables. Generalizability of this study was limited
because I only drew participants from the United States; the theoretical perspective of
Bowen can also be viewed as a delimitation. Also, I did not include sexual
inappropriateness, sexual transference, and sexual counter-transference in this study, nor
did I include criteria regarding sexual orientation because they were beyond the scope of
this study.
Limitations
Pyrczak and Bruce (2000) defined a limitation as a “weakness or handicap that
potentially limits the validity of the results” (p. 57). In this study, there were limitations
related to internal validity, including methods of sampling, instrumentation, testing, and
administration. Even with a random sample, the level of control is reduced because of the
design being quasi-experimental and not purely experimental (see Campbell & Stanley,
1966). Regarding testing and survey administration, this study was not on par with any

12
study that included in-person methods to collect data, and because the study was web
based, nonresponses may have increased due to lack of access or inability to understand
how the survey link and Survey Monkey system works (see Millar & Dillman, 2011).
Internet surveys are affordable and efficient and allow a broad reach that might not
otherwise be possible, which made them a good fit for this study despite the limitations
(see Ward, Clark, Zabriskie, & Morris, 2012). Additional limitations of this study were
that therapists may have felt they must provide the politically correct or socially
enlightened answer that did not reflect their true perspective. Also, a more conservative
or traditional therapist may have avoided answering certain survey questions because of
their potential for being too personal in nature; this may have also led therapists to not
return the survey or to exit the survey early because they did not want the information to
be known even though I assured them anonymity.
Significance
Therapists need to be willing to initiate and discuss with clients, their sexual
health issues (LoFrisco, 2013). Because this is not occurring on a regular basis, I
conducted a study to address how the therapy community may increase the willingness of
therapists to discuss sexual issues with their clients. Anderson (2002) asked “what effect
does the combination of the variables of human sexuality knowledge, experience, and
attitudes have on the sexual comfort” (p. 8) and willingness to engage clients in
discussions of sexuality? I attempted to answer this question to further the understanding
in this area. Few researchers have delved into this area, and this gap in understanding
negatively impacts millions of Americans who rely on marriage and family therapists for

13
guidance when dealing with sexual health issues (Cupit, 2010; Dermer & Bachenberg,
2015; Harris & Hays, 2008; Juergens et al., 2009; LoFrisco, 2013; Papaharitou et al.,
2008; Timm, 2009). The results of this study may inform the marriage and family therapy
community education curriculum used to prepare therapists in school and postgraduate
studies, and the results of this study may inform the training methods used in workshops,
supervision, and clinical settings to prepare therapists through understanding of the
elements that impact their willingness to discuss sexual health issues with a client (see
Cupit, 2010). Therapists may use the results from this study as a basis for positive change
within the marriage and family therapy community by addressing a problem and
suggesting potential solutions so that the population that is suffering from sexual
dysfunction may be better served.
Summary
Chapter 1 provided an overview of the scope of this study concerning marriage
and family therapists and the pressing concern that therapists are not initiating and
engaging in discussions with their clients regarding sexual health issues. The potential for
harm to the client formed part of the basis for this study; the other was the dearth of
literature in this area. I reviewed the independent variables addressed in this study
(knowledge, with its subsets of training, supervision, clinical experience, and attitudes)
and the dependent variables of comfort and willingness to engage and discuss with a
client regarding a sexual issue. I described the quantitative correlational research design,
including the survey method. The survey comprised instruments that were reliable and
valid, and I analyzed data using multiple regression analysis. The results from this study

14
may be used to start a conversation within the marriage and family therapy community in
hopes that educational institutions will take note and better prepare marriage and family
therapists for practice. Findings may also be used to improve the care provided by those
in practice. In Chapter 2, I review the literature from other disciplines in addition to the
marriage and family therapy discipline to provide an in-depth perspective on the issues.

15
Chapter 2: Literature Review
A current problem within the community of marriage and family therapists is a
lack of knowledge, comfort, and willingness to engage clients about their sexuality
(Dermer & Bachenberg, 2015; Harris & Hays, 2008). Therapists are not engaging their
clients regarding sexual health issues because of lack of comfort; avoiding or dismissing
the issue can result in damage to the client (Cupit, 2010; Harris & Hays, 2008; Juergens
et al., 2009; LoFrisco, 2013; Papaharitou et al., 2008; Timm, 2009). The purpose of this
study was to examine the relationship between the independent variables of therapists’
attitudes and knowledge and the dependent variables of therapists’ comfort with sexual
topics and willingness to discuss sexual topics. A better understanding of how these
variables interact with each other during the process of therapeutic discussions of
sexuality from the therapists’ perspective may provide a significant addition to the body
of research in this area.
Synopsis of Current Literature
Haesler, Bauer, and Fetherstonhaugh (2016) studied health care professionals’
attitudes and knowledge regarding sexuality and found a lack of confidence and
knowledge in providing treatment to patients; many health care professionals in their
study considered sexuality to be outside the scope of their practice, while still indicating
“that a positive and respectful attitude toward sexuality is important” (as cited in
Saunamäki, Andersson, & Engström, 2010, p. 1308). Haesler et al. (2016) found that
therapists’ knowledge and attitudes were significant contributors to predicting how
therapists interacted with clients regarding sexuality. Although health care professionals

16
as a group considered sexuality to be an important part of the human experience, many
did not wish to provide treatment in that area for their clients (Verschuren, Enzlin,
Geertzen, Dijkstra, & Dekker, 2013). According to Cupit (2010), there has been a steady
decline in research in the area of sexuality since the 1970s. Dermer and Bachenberg
(2015) found that marriage and family therapists have not made any significant progress
in the past 40 years, and that their comfort has not improved regarding sexuality as a
topic. Russell (2012) examined counselors’ attitudes and knowledge about sexuality as a
topic and found that attitude was the primary predictor of whether counselors addressed
sexuality with clients. The first researchers to address therapists’ comfort and willingness
to engage in topics of sexuality were Harris and Hays (2008). Since then, several other
researchers have examined different groups—primarily counselors and psychologists—
about several relevant variables, but no study has addressed all four variables as applied
to the marriage and family therapist community. Given the importance of human
sexuality to the individual, the prevalence of sexual dysfunction presently occurring in
both men and women, and the therapeutic setting offering the only available resource for
individuals, broadening the understanding of this issue is important to encourage more
effective practice among marriage and family therapists (Bancroft, 2009a; Harris & Hays,
2008; Laumann et al., 2007; Lyons, Bieschke, Dendy, Worthington, & Georgemiller,
2010; Shifren, Brigitta, Russo, Segreti, & Johannes, 2008).
Chapter 2 starts with a discussion of the research strategy employed in compiling
this literature review, along with key terms used and databases accessed. I discuss the
theoretical foundation upon which I based this study—Bowen’s theory (see Kerr &

17
Bowen, 1988). Bowen posited that anxiety held therapists back from discussing sexual
topics with clients (Harris & Hays, 2008; Kerr & Bowen, 1988). Following the
presentation of the theoretical foundation, I discuss each variable (knowledge, attitude,
comfort, and willingness to engage) within several subsections of health care
professionals, including counselors, therapists, and psychologists. I explain the
importance of these variables to therapeutic practice, their relevance to this study, the gap
in the literature, and the need for further study. I conclude with a summary.
Literature Research Strategy
I conducted multiple searches using the following databases: Academic Search
Complete, Dissertations and Theses, Dissertations and Theses at Walden University,
ERIC, Expanded Academic ASAP, MEDLINE (with full text), ProQuest Central,
ProQuest Health & Medical Complete, ProQuest Nursing & Allied Health Source,
PsycARTICLES, PsycINFO, PubMed, SAGE Premier, SocINDEX (with full text),
Taylor and Francis Online, and Thoreau Multi-Database Search. I also used the Google
Scholar search engine. The key words used in the literature review included counselor,
therapist, psychology, psychologist, therapy, marriage and family therapy/therapist,
nurse, nursing, medical, health care, allied health, health care professional, and
physician. I combined these search terms with the words sex, sexuality, attitude, comfort,
knowledge, approach, willingness to engage, and discussion. For example, one search
included the words “therapist attitude sexuality.” Appendix A provides a detailed list of
search terms.

18
I used the same databases to search for Bowen’s theory related to sexuality in a
therapeutic context. Most authors published their materials within the last 5 years.
Although this filter was typically viable in the area of medicine and health care, other
areas lacked relevant literature within the 5-year parameter. Peer-reviewed journal
articles constitute most of the literature cited in this chapter. I also review doctoral
dissertations, textbooks, and handbooks.
Because the focus of this study was sexuality and how it is addressed in a
therapeutic setting, sex, sexuality, and sexual issues are thoroughly defined and reviewed.
I included all available research in the area of marriage and family therapists’ comfort,
knowledge, attitudes, and willingness to discuss sexual issues with clients. In the area of
marriage and family therapy, the seminal work was Harris and Hays’s (2008) study
regarding therapists’ comfort and willingness; this was the only peer-reviewed research
related to this area as applied specifically to marriage and family therapists. Miller and
Byers (2012) conducted important research regarding psychologists, a different type of
mental health professional. Similar to Cupit (2010), I found limited literature available on
these subjects, so I expanded my review beyond the marriage and family therapy area to
include other health care professionals such as counselors, psychologists, and
rehabilitation counselors, which proved helpful and illustrative of the issues facing the
marriage and family therapy community.
Theoretical Foundation
Bowen (1976) developed a family systems theory based on his work as a
practicing family therapist, observing clients in both structured and unstructured settings.

19
The major theoretical constructs of Bowenian theory appropriate for this study were
anxiety and reactivity (see Cupit, 2010; Harris & Hays, 2008, Schnarch, 1998). When
therapists’ emotional reactions interfere with their awareness, it is difficult to be helpful
in the therapeutic relationship (Kerr & Bowen, 1988; Schnarch, 1991). Schnarch (1991)
emphasized how important human sexuality was by stating that “the expression of
sexuality is a window into who each person is and how they relate to each other” (p. 20).
If therapists lose awareness of what is going on within the therapeutic relationship
because they have become anxious and allowed their emotions to stop or severely impede
the process, they not only impair the process with clients but “also could perpetuate the
symptoms of the problem within the system” (Harris & Hays, 2008, p. 241). This lack of
awareness causes the exact type of harm that Cupit (2010) and LoFrisco (2013) stated
should not occur in the therapeutic relationship. The way that therapists have dealt with
this anxiety is by not addressing the topic (Cupit, 2010; Harris & Hays, 2008; LoFrisco,
2013; Schnarch, 1991; Yelton & Delfin, 2015). It is imperative that the therapist is
relaxed when initiating the discussion about sexuality, and the therapist needs to be aware
that the client is often waiting for the therapist to initiate the discussion (Harris & Hays,
2008; Hays, 2002). For an individual to become a fully integrated sexual being, the
therapist must act as the model of how to move past the anxiety that is acting as a barrier
to progress (Harris & Hays, 2008; Schnarch, 1991, 1998). Harris and Hays (2008)
applied Bowen’s theory in their research, which addressed the relationships “between
therapists’ sexual knowledge and their comfort with sexual material and how these

20
factors influenced the likelihood that the therapists will engage in sexual discussions with
their clients” (p. 241).
Cupit (2010) chose Rogers’s (1951) person-centered theory of self-actualization
as the lens through which to analyze the subject of counselors’ comfort and willingness to
discuss sexual topics with clients. Cupit also used four of the instruments developed by
Harris and Hays (2008) in her study design. Cupit and LoFrisco (2013) both cited the
lack of research that continues to negatively impact this area, a circumstance that led
Cupit (2010) to use the Harris and Hays (2008) instruments.
I chose the Bowenian theory for the current study to further Harris and Hays’s
(2008) seminal research and to stay within the framework they established on this topic. I
also chose Bowenian theory to address the main issues reported by therapists in
discussing sexuality with clients: that they feel anxious, emotionally unready, and
reactive about starting a discussion about a client’s sexual health. Kelsey, Stiles, Spiller,
and Diekhoff (2013) found that 52% of therapists do not view themselves as competent to
discuss bondage, dominance, sadism, and masochism with clients and would refer a
client presenting with this issue to someone else.
The Bowenian theory was appropriate for the present study because it was the
only theory chosen by Harris and Hays (2008). Moreover, there had not been any
research done in this area since the Harris and Hays study. The Bowenian theory
provided the best lens to understand anxiety and emotional reactivity on the part of the
therapist when discussing sexual topics with clients. Also, Bowenian theory provided
continuity to the reader by building on the framework developed by Harris and Hays

21
(2008). The research questions related to Bowenian theory focused on the influence the
perceptions of sexual knowledge have on therapists and how to increase their feelings of
competency. I included attitude as the missing variable to provide a clearer picture of
what factors influence therapists in their willingness to engage clients in a discussion
about sexuality.
Sexuality
Sexuality is an important aspect of people’s lives and a major component of
mental health for the client (Bancroft, 2009a; Cupit, 2009; Lyons et al., 2010). Human
sexuality “encompasses gender identities and roles, sexual orientation, eroticism,
pleasure, intimacy, and reproduction” (WHO, 2006, p. 5). Diamond and Huebner (2012)
supported the links between well-being and sexuality and between the quality of life and
sex life of a couple. An individual’s sexuality is a human right that the therapist should
cherish and nurture. However, the ideological background of the therapist can inhibit
open discussion (M. S. Green, Murphy, & Blumer, 2010).
Shifren et al. (2008) found that 43% of adult women suffered from ongoing,
regularly recurring sexual dysfunction. This rate varied depending upon which
dysfunction was being measured (arousal, interest, lubrication, or failure to orgasm) ,but
the incidence at which these dysfunctions occurred appeared to support previous research
(McCabe et al., 2016). Because of the small amount of literature on this topic, however, it
was difficult to assess the scope of female sexual dysfunction in the United States
(McCabe et al., 2016).

22
Men were also likely to have sexual dysfunction issues, with 22% over age 40
suffering from erectile dysfunction (Laumann et al., 2007). If a sexual issue remained
unresolved, the potential consequences were less happiness for the individual, which then
impacted his or her well-being (Rosen & Bachmann, 2008). Despite the regularity with
which sexual issues occur and the negative consequences if sexual issues are not
addressed, there exists a systemic failure by the therapeutic community to address these
concerns (Harris & Hays, 2008; Juergens et al., 2009; Papaharitou et al., 2008;
Weerakoon, Sitharthan, & Skowronski, 2008). Cupit (2010) noted the steady decrease of
research on the topic of sexuality since the 1970s.
In the Diagnostic and Statistical Manual of Mental Disorders (DSM–5; American
Psychiatric Association, 2013), the authors have reorganized sexual disorders, and they
have merged or eliminated some categories entirely (Graham, 2016). For example, the
authors combined hypoactive sexual desire disorder and female sexual arousal disorder
into a single, broader definition: female sexual interest/arousal disorder (Graham, 2016).
In the same fashion, they merged dyspareunia and vaginismus into genito-pelvic
pain/penetration disorder (IsHak & Tobia, 2013).
Male hypoactive sexual desire disorder is now a category. The authors renamed
male orgasmic disorder as delayed ejaculation with broader definitions included and both
male dyspareunia and male sexual pain were removed (IsHak & Tobia, 2013). The
authors did not make these changes without controversy but reflected the most current
empirical research available (IsHak & Tobia, 2013). That the DSM-5 includes these

23
sexual disorders and syndromes and that the definition of specific disorders is still in flux
indicates the ongoing importance of human sexuality as related to psychotherapy.
Comfort
Health Care Professionals’ Comfort With Sexual Topics
Graham and Smith (1984) developed the following definition of sexual comfort
over 30 years ago: “Sexual comfort is a broad, complex construct involving cognitive,
affective, and behavioral responses to sexuality; as well as a developmental task
influenced by the physiological, psychological, sociological, spiritual or religious,
educational, and sexual aspects of one’s being” (p. 439). This definition continues to
provide a framework to determine the comfort level of therapists dealing with the topic of
sexuality with clients. Graham and Smith (1984) found that attitudes, feelings, and
communication skills had an impact on sexual comfort. Haboubi and Lincoln (2003), in
their survey of 100 doctors, nurses, occupational therapists, and physiotherapists found
that 90% of respondents agreed that sexual health was important and that they should
address it as part of the health care approach. Ninety-four percent of these health care
professionals would not initiate a discussion of sexuality with a patient due to lack of
comfort. Most felt poorly trained to handle a discussion regarding a patient’s sexuality
(Haboubi & Lincoln, 2003). These findings were similar to previous research, however,
about whether gender, attitude, or knowledge impacted this discomfort. Fifty percent of
the respondents cited embarrassment as a barrier to discussing sexual issues, even though
60% of respondents said that they would feel comfortable discussing sexual issues with
clients (Haboubi & Lincoln, 2003). In a more recent study of nurses, researchers found

24
that 66% felt comfortable discussing sexual issues with patients (Saunamäki et al., 2010).
Older nurses were more confident and comfortable discussing patients’ sexual issues and
concerns and also displayed a more positive attitude toward sexuality and dealing with
sexual health. In a similar study, 67% of nurses felt comfortable discussing sexual issues
with patients, but only 40% felt the need to do so; 33% did not feel comfortable initiating
the discussion or discussing sexual health issues with patients (Kotronoulas,
Papadopoulou, & Patiraki, 2009). In an earlier study, Magnan and Reynolds (2006) found
that OB/GYN and rehabilitation nurses were more comfortable than their other nursing
specialization peers and noted certain specializations as a barrier to discussing sexual
issues with patients.
Lack of comfort and failure to address sexual issues was also found in surveys
involving physicians, but was more pronounced in geriatric care, female-specific care,
and disabilities (Haboubi & Lincoln, 2003; Maciel & Laganà, 2014; Pauls et al., 2005;
Thomason, Capps, Lefler, & Richard-Davis, 2015). In a qualitative study of physicians
from the United Kingdom, Dyer and das Nair (2013) found that physicians were not
comfortable initiating conversation with patients regarding sexual issues due to personal
discomfort and a fear of “opening up a can of worms” (p. 2658). Physicians also noted a
greater challenge when addressing sexuality with minority groups, including Blacks,
nonheterosexuals, people with disabilities, and the aging (Dyer & das Nair, 2013).
Verschuren et al. (2013) found that 67% of the 177 health care professionals surveyed
had not addressed sexuality with patients. The authors discovered this particular group of
physicians and rehabilitation professionals ranked high on the comfort index; however,

25
the majority did not consider it their role to discuss sexual issues with patients being
fitted for prosthetics.
Kazukauskas and Lam (2010) found that comfort was at a medium level for
rehabilitation health care professionals. They also found a correlational link between
attitudes and knowledge impacting the comfort of the rehabilitation health care
professional when approaching and discussing sexual topics with patients.
Helland, Garratt, Kjeken, Kvien, and Dagfinrud (2013) found that Rheumatology
physicians who had sexuality-specific education were more comfortable discussing the
associated topics with patients. Higgins et al. (2012) found that when health care
professionals engaged in a one-day program geared toward an interdisciplinary approach
to sexuality, participant comfort levels regarding sexuality increased. In a longitudinal
mixed methods study of 37 rehabilitation practitioners that comprised of 23 nurses, ten
community staff, three allied health and one medical practitioner, researchers found that
comfort did not change significantly over time between the control and experimental
group. Nevertheless, comfort did increase over a 2-year period (although the authors did
not proffer an opinion about why) (Fronek, Kendall, Booth, Eugarde, & Geraghty, 2011).
Counselors’ and Therapists’ Comfort With Sexual Topics
Sexual comfort impacts every aspect of the client’s being and the comfort level of
counselors and therapists in discussing sexuality with their clients should be of prime
importance (Graham & Smith, 1984). As the counselors’ knowledge of sexuality
increase, their comfort levels increase as well (Graham & Smith, 1984). Haboubi and

26
Lincoln (2003) found that doctors and nurses were more comfortable discussing sexual
topics with patients than therapists were with their clients.
If clients felt that their therapists were not comfortable with the topic of sexuality,
that discomfort could damage the therapeutic relationship, make the topic taboo, or
alienate clients from the help they need (Cupit, 2010). In a study of counselors, Anderson
(2002) analyzed the variables that impact comfort and found a positive correlation
between experience and comfort: The more years in practice correlated with greater
comfort in discussing sexual topics. However, the largest predictor variable of comfort
was the counselor’s attitude toward sexuality; therapist instructors were encouraged to
promote more liberal sexual attitudes among their student therapists (Anderson, 2002).
In research involving mental health counselors, participants reported being
comfortable with sexual topics, but that did not correlate with how frequently they
initiated those topics with clients (LoFrisco, 2013). The research also reported that
counselors who often initiated sexual conversations with clients also had a higher level of
comfort with sexuality.
Sexuality is a sensitive topic and several researchers have determined that
therapists’ and counselors’ levels of comfort in discussing sexual topics with clients need
to increase so that they can address clients’ sexual concerns (Harris & Hays, 2008; Hartl
et al., 2007; Papaharitou et al., 2008; Weerakoon et al., 2008). Counselors prepare to
initiate sexual discussion and normalize it because they cannot assume that “…clients
will initiate a discussion about sexual health issues even when it is an area of concern for
them” (Hays, 2002, p. 4).

27
LoFrisco (2013) pointed out that there is little empirical research on how the
willingness component of the process can increase. Furthermore, the research done to
date to find a connection between knowledge and comfort has been conflicting. Harris
and Hays (2008) did not find a connection, nor did Decker (2010), which corroborates
previous findings by Ford and Hendrick (2003). However, Haag (2008) and Weerakoon
et al. (2008) did, in fact, find a positive correlation between knowledge and comfort in
direct contradiction to the other researchers.
Harris and Hays’s (2008) study was the only one exploring the relationship
between comfort and knowledge and how these impact therapists’ willingness. However,
they did not measure test–retest reliability or content validity and used low-reliability
portions of their instrument. Haag (2008) used no reliability or validity measures.
Comfort is not just an aspect of how the therapist and counselor view the topic of
sexuality, but also impacts how the counselor addresses an individual belonging to a
sexual minority (M. S. Green et al., 2010). Student counselors were uncomfortable when
addressing issues with lesbian and transgender couples (Rutter, Leech, Anderson, &
Saunders, 2010). Therapists who support civil unions and human rights are more
comfortable discussing sexual topics with gay, lesbian, bisexual, and transgender (LGBT)
individuals, but less comfortable when discussing sexual topics with couples (M. S.
Green et al., 2010). This result was supported by the research of Juergens et al. (2009)
and M. S. Green et al. (2010), who found that therapists’ attitudes impacted comfort.
Kazukauskas and Lam (2010) found that knowledge and attitude were significantly
correlated with comfort on the part of the counselor engaging the patient to discuss a

28
topic regarding sexuality. In a more recent study, Pebdani (2013) tried to determine what
correlations could be established regarding rehabilitation counselors and found that
knowledge had a negative correlation to discomfort. As sexual knowledge increased,
discomfort levels decreased.
Pukall (2009) argued that the therapist who was not comfortable discussing
sexual health issues could not provide effective therapy. Therapists’ or counselors’
discomfort in discussing sexual topics was a significant barrier in the ability of clients to
establish a therapeutic alliance with them and receive quality care (Bancroft, 2009b;
Kazukauskas & Lam, 2010; Moser, 2009; Nasserzadeh, 2009). Donovan (2011) and
Cupit (2010) both found that proper supervision and training helped to increase comfort
for the therapist or counselor, and thereby, diminished this barrier.
Voss (2015) found that comfort for therapists and counselors who dealt with
sexual topics impacted competencies. Therefore, comfort was an important facet of
therapists’ relationships with clients. Easton’s (2015) research involving rehabilitation
counselors working with patients with autism found they were more comfortable when
addressing general sexual issues than when addressing sexually-explicit topics (such as
masturbation). For the community of marriage and family therapists and counselors as a
whole, there has been little overall improvement in comfort regarding discussion of
sexuality over the past 30 years (Dermer & Bachenberg, 2015).
Psychologists’ Comfort With Sexual Topics
Clinical psychology students were the participants in three studies regarding
sexuality and comfort (Hanzlik & Gaubatz, 2012; Miller & Byers, 2012; Zimmerman,

29
2015). Hanzlik and Gaubatz (2012) did a cross-sectional study of 138 clinical PsyD
students to assess their comfort levels when dealing with clients’ sexual issues. Hanzlik
and Gaubatz found that trainees had lower levels of comfort when discussing specific
sexual concerns but had higher levels of comfort “when asked globally about discussing
sexual issues with clients” (p. 219). These researchers also found that trainees had similar
levels of comfort in discussions of sexuality with female clients, but female trainees had
lower levels of comfort compared to their male peers when discussing sexual issues with
male clients. Hanzlik and Gaubatz found a positive correlation between sexual attitudes
and comfort and between sexual training and comfort but did not find any correlations
between general education and comfort.
Zimmerman (2015) found that 85.1% of the clinical psychology student
participants in their study were comfortable with transgender clients but had insufficient
training to help implement action for these clients. Miller and Byers’s (2012) study
design included psychologists and their findings indicated that with sexuality-specific
education and supervision, participants’ confidence and self-efficacy—variables related
to comfort—increased.
Attitudes
Health Care Professionals’ Attitudes Toward Sexual Topics
Sexuality and sexual health are a priority in the treatment of patients (Cupit, 2010;
Helland et al., 2013; Verschuren et al., 2013). Verschuren et al. (2013) found that two-
thirds of physician participants in their research thought sexuality was important, but only
one-third considered it part of their duties to engage the patient in sexual topics. These

30
researchers coined the term conspiracy of silence to indicate a dynamic in which both the
physician and the patient avoid potentially awkward discussions about sexuality
(Verschuren et al., 2013). Similarly, Helland et al. (2013) found that 96% of health care
providers involved in rheumatological care considered sexuality to be a relevant topic,
but 71% of these participants rarely or never raised the issue while 88% thought the
patient should initiate this topic.
In the past decade, there has been a positive shift in the attitudes of health care
workers regarding sexuality and the treatment of individuals who are members of the
LGBT community (McCune, Imborek, Ho, Hardy-Fairbanks, & Stockdale, 2015). For
my purpose, “the definition of attitude involves an emotional expression of what we
value, believe in, and what we consider to be ‘right’” (see Stuart, 2014, p. 23).
Nicol, Chapman, Watkins, Young, and Shields (2013) had similar results.
Attitudes of health care professionals were significantly impacted by “…professional
group, gender, Caucasian race, political voting behavior, presence of religious beliefs, the
frequency of attendance at religious services, the frequency of praying, and having a
friend who was openly lesbian, gay, bisexual and transgender” (p. 3396). Wilson et al.
(2014) found that religiosity and familiarity with sexual issues and LGBT issues were
predictive of less positive attitudes toward sexuality, treatment of sexual health issues,
and dealing with LGBT patients with the 475 mental health students who participated in
their survey.
Universally positive and open-minded attitudes toward sexuality were not the
norm, however. For example, Malaysian medical student participants held conservative

31
beliefs and did not wish to engage with patients on various sexual health topics (Sidi et
al., 2013). A recent study of Brazilian OB/GYN medical students revealed conservative
attitudes as well (Vieira et al., 2015).
Turkish nurse participants held conservative, negative attitudes toward sexuality
and discussing sexual issues with patients (Arikan, Meydanlioglu, Ozcan, & Ozer, 2015).
However, Bal and Sahiner (2015), who conducted a similar study of 155 Turkish nurses
in the same year, found these negative and conservative attitudes could improve with
proper, sexuality-specific training. In contrast, male medical students in India held neutral
attitudes toward homosexual patients, homosexuality, and discussing sexual topics with
non-heterosexual patients while female medical students held positive attitudes (Banwari,
Mistry, Soni, Parikh, & Ghandi, 2015). These researchers noted a lack of sexual
knowledge among participants, which they attributed to underlying attitudes; other
research echoed this analysis (Banwari et al., 2015; Sidi et al., 2013).
Studies focused on nurses’ attitudes have been evenly split. For example, in their
research with nurses, Kotronoules et al. (2009) found that participants had positive
attitudes toward sexuality. In contrast, others found negative attitudes among their
nursing participants toward sexuality and dealing with sexual health issues (Chapman,
Watkins, Zappia, Nicol, & Shields, 2012; Eliason, DeJoseph, Dibble, Deevey, & Chinn,
2011). Based on the data collected from nursing students, Strong and Folse (2015) found
negative attitudes when participants discussed sexuality with patients in the LGBT
community. Attitudes improved significantly, however, after an intervention was
administered to these student nurses (Strong & Folse, 2015). Likewise, Tugut and

32
Golbasi’s (2015) research noted this effect in nurses when attitudes, knowledge, and
behaviors improved after receiving specific sexuality assessment skills training. Sung and
Lin (2013) found among their nurse participants in a quasi-experimental study with a
control group that sexuality-specific training positively affected attitudes, beliefs, and
behaviors. Sung, Huang, and Lin (2015) found a relationship between knowledge and
attitude and the importance of not only educating nurses with sexually specific training to
improve knowledge, but also to stress the importance of a positive attitude toward sexual
health issues when dealing with patients.
Lapinski, Sexton, and Baker (2014) found that osteopathic medical students had
positive attitudes toward sexual minority patients when discussing sexual issues and
treating them; participants who self-identified as LGBT had even higher positive scores
in the attitude category regarding discussion and treatment. However, these osteopathic
students were unequipped to treat the LGBT population; the researchers recommended
LGBT sexuality-focused education to remedy this deficit among this category of health
care practitioners (Lapinski et al., 2014).
The data from nonwestern, non-North American midwives showed participants to
have positive attitudes toward sexuality, discussing sexual topics with patients, and
providing counseling on sexual topics. However, this was a single study, and the data
may not be generalizable to the field of midwifery (Khadivzadeh, Ardaghi, Mazloum, &
Modaresi, 2016). These participant midwives were also inadequately trained and had a
significant lack of sexual knowledge (Khadivzadeh et al., 2016).

33
Valvano et al. (2014) found a general difference among 479 members of various
health care disciplines regarding educational quality and quantity. There was also a wide
variation of attitudes with dentists having the most negative. Based on their research,
34% of medical students and 98% of psychology students had no patient contact
regarding sexual health issues. Valvano et al. (2014) stressed that negative attitudes could
have an undesirable impact on patients, while attitudes toward sexual health issues
among health care professionals seemed to be positive; these attitudes linked to sexually-
specific health training. They argued that it was important to provide this type of training
(Valvano et al., 2014).
Physician’s assistants had liberal attitudes toward sexuality, with the majority
(64%) holding these liberal attitudes, 35.4% holding neutral attitudes, and 0.6% holding
conservative attitudes (Wolf, 2012). Two factors significantly impacted the physician’s
assistants’ attitudes: ethnicity and relationship with religion. Wolf (2012) urged students
to examine their sexual beliefs and attitudes due to the impact those beliefs and attitudes
would have on their ability to assist patients with their sexual health issues. Wolf’s
(2012) question on religion was a simple “yes” or “no” question as to whether the
participant considered themselves to be religious. In contrast to Wolf’s findings, Cupit
(2010), in her study of counselors, did not find any statistically significant relationships
between her independent variables and religion. I did not find any other studies in my
literature review that included the variable of religion. Harris and Hays (2008) suggested
that religion was a variable that should be included in future research, which is why Cupit
(2010) included it as a single item on a Likert-type scale of 1 to 5 in her research.

34
Health care professionals’ attitudes toward the sexuality of their older patients
were markedly different between people working in nursing home medical facilities and
those working in hospitals (Doll, 2013). Thirty-two percent of the nursing home
administrators and nurses reported that they would be disgusted to discuss sexuality with
a patient, while 20% stated that they would panic, and “20% would ignore the behavior”
(Doll, 2013, p. 59).
Haesler et al. (2016) conducted a systematic review of 23 studies concerning
health care professionals’ knowledge and “attitudes toward sexuality and sexual health of
older people” (p. 65) that they published during an 11-year period (2004 to 2015). The
authors concluded that practitioners were still reluctant to engage older patients on their
sexuality due to attitudes influenced by negative and less permissive societal attitudes and
lack of knowledge.
Moreno, Gan, Zasler, and McKerral (2015) found that physicians treating
traumatic brain injuries thought that sexuality was important and had positive attitudes
toward discussing it. However, they did not discuss sexuality with patients. The
physicians who treated traumatic brain injuries had more positive and permissive
attitudes than other participants who included family care physicians, psychologists,
general practitioners, and other highly educated health care professionals (Moreno et al.,
2015).
These various researchers who had focused on the attitudes of health care
professionals regarding sexuality and discussing sexual topics with their patients had

35
reached different conclusions. Results were influenced by the area, specialty or discipline
in question, geographic region, and cultural background of participants.
Counselors’ and Therapists’ Attitudes Concerning Sexual Topics
Attitudes are concepts that therapists apply to social objects that have a firm base.
Conversely, the values held by therapists tend to focus more on ideals (Hitlin & Piliavin,
2004). Several researchers have concluded that therapists avoid sexual discussions due to
lack of comfort (Harris & Hays, 2008; Shalev & Yerushalmi, 2009; Timm, 2009). It is
assumed that greater knowledge would equate to greater comfort. However, attitude is
another important component of the process that can lead to comfort and willingness to
discuss sexual health issues (Papaharitou et al., 2008). Personal values and experiences
influence attitudes toward sexual issues; through training and self-awareness, comfort can
increase, anxiety can decrease, and willingness to engage can begin (Hilton, 1997). While
authors conducted a number of studies in the late 1990s and early 2000s (as reviewed in
the following paragraphs), a lack of new literature exists on attitudes, knowledge,
practices, and behaviors concerning engaging clients in sexuality discussions among
marriage and family therapists and counselors (Dunk, 2007; Yelton & Delfin, 2015).
In her research of 310 licensed counselors in three different states, Anderson
concluded that a “combination of factors influenced counselors’ sexual comfort and
willingness to engage clients about sexual health issues ” (as cited in Cupit, 2010, p. 23).
Most impactful were sexual attitudes, training and experience, and personal experience.
Harris and Hays (2008) addressed several of these components and determined that
supervised experience and training, along with knowledge, improved sexual comfort.

36
Juergens (2006) found that sexuality education and knowledge impacted attitudes and
attitudes impacted comfort. Cort et al. (2001) identified negative attitudes as a major
barrier that prevented the discussion of sexuality with clients. Hilton (1997) found that
counselors’ comfort was linked to their attitudes about sexuality and their knowledge-
base about sexuality. Similarly, Weerakoon and Stiernborg (1996) found a positive
relationship between sexual attitudes and knowledge. This, in turn, influenced sexual
comfort.
If the therapist’s perception of the patient’s sexual attitudes and values appeared
to be of a nontraditional making, the therapists were less likely to engage the clients in
sexual discussions (Weerakoon & Stiernborg, 1996). Negative bias in this area was why
it was important for therapists to understand their attitudes regarding sex and sexuality
(Stayton, 1998). As therapists increased their awareness, it became more likely they
would also decrease the likelihood of negatively viewing patients and causing discomfort
or harm (Stayton, 1998; Ridley, 2006). Based on this exploration of attitudes, therapists
improved their interactions with patients and avoided imposing a negative belief system
regarding sexuality onto the patient (Weerakoon & Stiernborg, 1996).
Once therapists understood their sexual attitudes, they were able to create a safe,
non-judgmental environment for the client in which—due to the comfort—the client was
more open and engaged (Andrews, 2000). Anderson (2002) found that attitude impacts
personal bias and attitude, and values were only ascertained and adjusted by awareness.
Knowledge was a combination of training and education, and these two components
impacted sexual comfort and willingness to discuss sexual health issues. Even those who

37
did not believe that knowledge impacted comfort found that was one of the important
issues in understanding how to improve comfort and willingness to engage (Anderson,
2002). West et al. (2012) found a link between knowledge, comfort, and attitudes toward
sexuality as well as a correlation between religiosity and negative attitudes. West et al.
also found that social, economic, and gender factors impacted attitudes, further
underscoring how complex and complicated attitudes were in their nature. Similarly,
Procter (2013) found that religiosity and religious fundamentalism were predictive of
negative attitudes toward LGBT clients and damaged the therapeutic alliance. Negative
attitudes also impacted how likely the therapist was to refer a lesbian, gay, or bisexual
client for services, according to other research (McGeorge, Carlson, & Farrell, 2015).
In Goldstein’s (2014) study with 100 students in a Council for Accreditation of
Counseling and Related Educational Programs’ (CACREP) course, she found that the 60
master’s students had less positive attitudes toward transgender and LGB clients than did
the 40 doctoral students. The author did not discover a reason for that occurrence but
hypothesized that multicultural classes taken by only the doctoral students might have
impacted these results. Both masters and doctoral students in both psychology and
counseling exhibited positive attitudes toward counseling transgender clients (Goldstein,
2014).
In their study with marriage and family therapists, psychologists, and social
workers, Alessi, Dillon, and Kim (2015) found no differences in attitudes toward gay and
lesbian clients, “even after controlling for years of practice experience and age” (p. 455).
Rather, it was the level of training that was associated with and indicative of a more

38
positive attitude, self-efficacy, and positive beliefs. Kelsey et al. (2013) studied
therapists’ attitudes toward bondage, discipline, sadism, and masochism (BDSM) and
found that those with more training had more positive attitudes toward treatment and
discussion of BDSM with clients. Forty-eight percent of therapists viewed themselves as
competent, while 52% did not; therapists with more experience treating clients who
engaged in BDSM had more positive attitudes than those who did not have as much
experience (Kelsey et al., 2013).
Farmer, Welfare, and Burge (2013) found that counselors in a variety of settings
had positive attitudes toward the LGB community but lacked the knowledge and
competency to engage their LGB clients about their sexual issues. Parker (2012) found a
similar connection between attitudes and training in that the more sexuality-specific
training a high school counselor had received, the greater their positive attitudes toward
discussing sexual topics with students who also had intellectual disabilities. Furthermore,
the level of comfort a high school counselor had to discuss sexuality with students, the
more positive his or her attitude was toward discussing sexuality (Parker, 2012).
Psychologists’ Attitudes Concerning Sexual Topics
Psychologists’ attitudes toward discussing sexual topics correlate with comfort.
With permissive attitudes, their comfort levels increased (Hanzlik & Gaubatz, 2012).
Attitudes did not only impact comfort, but also their willingness to engage clients
regarding a sexual topic (Flaget-Greener, Gonzalez, & Sprankle, 2015). Flaget-Greener et
al. (2015) did not find any link between attitudes and sociodemographics (age,
sex/gender) clinical education, experience, and specialty in research involving 119

39
doctoral-level psychologists. Findings in other disciplines showed results in which those
variables were impactful. “This…may be explained by the [educational] homogeneity”
(p. 19) of the survey participants: Higher levels of education equate with higher levels of
permissiveness. These findings were in line with previous research done by Miller and
Byers who stated that “a key finding of this study is that attitudes toward sexuality
education and training are significant predictors of psychologists’ willingness to assess
sexual health” (as cited in Flaget-Greener et al., 2015, p. 20).
Johnson and Federman (2014) also found that attitudes impacted psychologists in
their approach to dealing with LGBT issues, including sexual issues, in their study of 384
Veterans Administration psychologists. They found that psychologists from more
broadminded regions in the US had more positive attitudes toward LGBT issues,
including sexual issues. Psychologists with more positive attitudes also had more training
and were open to pursuing more LGBT-specific training. Moreover, younger
psychologists who had received LGBT-specific training had more positive attitudes
(Johnson & Federman, 2014).
Moreno et al. (2015) found that psychologists had more negative attitudes toward
sexuality than did other health professionals. This is in slight contrast to what Alessi et al.
(2015) found: no difference in attitudes after controlling for age, practice years, and
sociodemographic information between family therapists, psychologists, and social
workers. However, given that Moreno et al. (2015) found that these negative attitude
levels were similar between the psychologists and social workers involved in their study,
this result did not contradict Alessi et al.’s findings. Also, Jabson et al. (2016) found that

40
psychologists and social workers as a whole had more negative attitudes when compared
to physicians.
Willingness to Engage
Health Care Professionals’ Willingness to Engage Patients
Physicians do not, as a whole, willingly initiate or engage in sexual topics with
their patients. Two studies found that most physicians did not ask sexual health questions
during intake visits, mostly due to a lack of training, which negatively impacted medical
students’ attitudes toward sexual health issues (Cushing, Evans, & Hall, 2005; St.
Lawrence et al., 2002). Rheumatology health care providers seldom or never raised
sexual topics 71% of the time. This result corresponded to other research in which 88%
of health care providers viewed it as the patient’s role to initiate discussions of sexuality
(Helland et al., 2013).
In another seminal study, Haboubi and Lincoln (2003) found that 94% of the
health care professionals surveyed would not initiate sexual discussions, even though the
overwhelming majority agreed that sexual health was important and should be addressed.
Furthermore, several researchers have found that general practitioners rarely ask about
sexual health issues, which correlated with a lack of sexuality training (Byrne, Doherty,
McGee, & Murphy, 2010; Laumann et al., 2009; Shepherd, Heke, & O’Donovan, 2009).
Stead, Br, Fallowfield, and Sealby (2003) came to a similar conclusion based on a “lack
of sexual knowledge and skills, as well as feelings of embarrassment, lack of time, lack
of privacy and lack of resources” (p. 670) as the prime reasons for doctors and nurses not
discussing sexual health with their patients. Patients perceived doctors as insensitive

41
when they avoided sexual health questions (Hinchliff, Gott, & Galena, 2005); this
perceived insensitivity made patients feel distressed (Dixon-Woods et al., 2002).
In Turkey, nurses were studied using a descriptive and comparative design;
researchers found that 68.9% of participants viewed the topic of sexuality as “too private
to discuss” with patients (Arikan et al., 2015, p. 327). The majority of these nurses
(72.2%) did not see the need to spend time discussing sexuality issues with patients.
These researchers used the Sexual Attitudes and Beliefs Scale (SABS) and found a
significant correlation between participant’s SABS scale score and willingness to discuss
sexual issues (the higher the score, the more likely the nurse was to discuss the issues).
Moreover, these authors recommended more education, which was a common theme
throughout most of the literature (Arikan et al., 2015).
Bal and Sahiner (2015) found similar results in their descriptive design studying
Turkish nursing students and determined that the barriers in discussing sexuality with
patients were insufficient time, training, or comfort. These researchers also used SABS
and found that 80% of nursing students were not willing to give advice even when the
patient started the discussion. They concluded that more education on sexuality was
necessary to develop this area of medicine (Bal & Sahiner, 2015). Dyer and das Nair’s
(2013) review of the literature about United Kingdom health care providers (doctors and
nurses) revealed an overall theme that health care providers were not interested in
bringing up topics of sexuality or engaging in discussion with patients about their sexual
health. In Sweden, a study using correlative and comparative design with the SABS
instrument using a convenience sample of Swedish nurses found 80% did not start

42
conversations with patients about sexual health issues and concerns. This number did not
correlate with the fact that 66% felt comfortable discussing the topic, according to the
survey results (Saunamäki et al., 2010). These researchers recommended more education
to improve the nurses’ abilities to engage in and provide holistic care to patients
regarding their sexual health issues.
The results of the Swedish study were not dissimilar from those found in a study
by Vieira et al. (2015) of Brazilian OB-GYNs in which 56% either never or rarely took a
sexual history, which would be a natural way to allow the possibility of a discussion
about sexuality with their patients. Fifty-one percent did not feel confident or competent
to take a sexual history or discuss the topic with a patient. Ninety-one percent of the
survey participants had graduated within the past five years and should have had the most
up-to-date training. However, 49% received no formal training, and 29% received 6
hours or less during residency. During their doctoral studies, 63.4% had received no
sexuality coursework, and 27.9% had 6 hours or less of sexuality coursework or
supervision. In other words, the inability for health care practitioners to discuss sex with
their patients is not only a Western or Eastern medicine issue but a global issue that needs
to be addressed (Vieira et al., 2015).
In a review of three decades of research with oncology nurses (18 articles) in a
meta-analysis, the authors found that oncology nurses rarely discussed sexual health
topics with patients for a variety of reasons: limited sexual knowledge, incorrect
assumptions, lack of comfort, and society-related factors (Kotronoulas et al., 2009).
Levesque (2013) used a descriptive design with convenience sampling to study nurse

43
practitioner students’ knowledge, attitudes, and self-efficacy. Levesque found that
students had positive attitudes, but little knowledge and low self-efficacy toward
transgender patients (i.e., they were unlikely to initiate the discussion with the patient).
Magnan and Reynolds (2006) studied barriers to discussing sexual health with nurses
across five nursing specializations (OB/GYN, oncology, medicine, surgery, and
rehabilitation) and found that nurses thought patients did not want them to discuss sexual
topics. This was the leading barrier across all nursing disciplines. The next major barrier
was lack of time.
Maciel and Laganà (2014) designed a study to examine a different aspect of the
sexual health discussion: How often did OB-GYNs discuss older women’s sexuality with
them? They found that two-thirds routinely asked patients about their sexual activity,
40% asked about sexual concerns or dysfunctions, and 29% asked about sexual
satisfaction. The authors noted that when clinicians did not raise sexual topics, the
patients determined that these topics were not appropriate and should not be discussed
causing further anxiety and unmet needs. Ninety-seven percent of the older female
participants wanted to discuss sexual issues with their treating OB-GYN (Maciel &
Laganà, 2014).
The Maciel and Laganà (2014) result was conflicting slightly with an earlier study
by Pauls et al. (2005) examining 471 member-physicians of the American
Urogynecologic Society. Sixty-eight percent were familiar with treating sexual
dysfunction in women, 47% thought sexual health screening for dysfunction was
somewhat important, and 42% believed it was important. However, 13% used

44
questionnaires for screening purposes, 22% always screened for dysfunction using
questionnaires or in-person discussion, 55% screened most of the time, and 23% never
screened or discussed sexual dysfunction with patients at all. The study authors stated
that sexual issues were reported at a higher percentage and were “more prevalent in
females (43%) than males (31%)” (p. 460).
Only 33% of physicians involved in the treatment of patients with amputations
addressed sexual health in any way (Verschuren et al., 2013). Verschuren et al. (2013)
used the Knowledge, Comfort, Approach, and Attitudes toward Sexuality Scale
(KCAASS) in a Dutch-adapted form to conduct their study. KCAASS was originally
developed for assessing physicians interacting with spinal cord injury patients.
Verschuren et al. (2013) analyzed the data by “using chi-squared-tests, independent
sample t-tests and one-way analysis of variance (ANOVA) with a least significant
difference (LSD) post hoc test.” Then, Verschuren et al. (2013) measured the effect size
using Cohen’s d and “Multivariate logistic regression analysis (stepwise backward) was
used to predict the odds of receiving a question about sexuality or address the issue of
sexuality” (p. 1699).
Moreno et al. (2015) examined how 16 men and 22 women who were, on
average, 2.6 years out from traumatic brain injuries, had experienced care regarding their
sexual health. The data revealed a low frequency of discussion about sexual health or
reproductive issues; their sexual needs went largely unaddressed and unmet. Participants
viewed the discussion of sexual topics as the treating physician’s role to raise with them

45
and not the role of a family physician, psychologist, general practitioner, or other health
care professionals (Moreno et al., 2015).
Counselors’ and Therapists’ Willingness to Engage Patients
There is a dearth of literature on the willingness of counselors and therapists to
engage clients in discussion of sexual topics (LoFrisco, 2013). Harris and Hays (2008)
did the original, seminal study prompting an ongoing conversation within the community
of therapists about how this variable impacted practice (Cupit, 2010; LoFrisco, 2013).
Harris and Hays (2008) did not make a distinction in their research, however, between
graduate-level supervision and postgraduate supervision of counselors. This distinction is
important due to the duration involved with each and is significantly different. Therefore,
level of education could impact the comfort and willingness to engage clients on sexual
issues.
Certified rehabilitation counselors who work with autism spectrum disorder
(ASD) patients were willing to discuss sexual topics with their patients and were
comfortable while discussing sexual topics with their patients (Easton, 2015). Gender
was not a factor in comfort or willingness; subjective normative beliefs, perceived
behavioral controls, and attitude were the variables that had strong correlations with a
willingness to engage as a whole. Attitudes toward sexuality and ASD did not have a
strong correlation. Easton (2015) reasoned that this outcome was influenced by the fact
that the framework used for the study had not been applied before and the sample was
small and homogenous. Easton encouraged further study using social cognitive theory as
the framework to examine counselors’ attitudes toward sexuality.

46
In their research with practicing certified rehabilitation counselors, Juergens et al.
(2009) found that “sexuality knowledge, sexuality education, attitudes toward the
sexuality of people with disabilities and comfort with sexuality affect the willingness of
rehabilitation counselors to discuss sexuality with clients with sexuality knowledge and
comfort with sexuality” had “direct effects on willingness among participants” (p. 113).
Cupit (2010) found that the more comfortable counselors were, the more likely
they were to engage the client. A significant correlation was found (r =.19, p<.01)
between sexual attitude (idealistic) and sexual comfort. Other sexual attitudes (i.e.,
attitudes toward birth control, sexual attitudes toward permissiveness and instrumentality,
strength of religion, and graduate specialization) did not result in a correlation.
Correlations were only found in the following variables with sexual comfort: sexual
attitudes regarding idealistic sexuality, human sexuality training, and supervision
experience in the area. While not all attitudes have a correlational relationship with
sexual comfort or with a willingness to engage, delineating which attitudes are associated
with a willingness to engage is important. Cupit found that the older counselors were, the
more willing they were to engage, while Harris and Hays (2008) found that age was not
impactful. This dichotomy of results is seen throughout the literature with some
researchers finding that gender or age was impactful, while others did not, suggesting the
need for further research. For example, Decker (2010) did not find a connection between
demographic variables, such as age, and willingness to engage, but did determine that
experience impacted and affected a therapist’s willingness to engage a client regarding a
sexual topic. Decker found that experience influenced comfort and that this had an impact

47
on willingness to engage; in contrast, age, experience, and training did not impact
comfort.
Yelton and Delfin (2015) found that 36% to 64% of mental health counselors
were willing to initiate a sexual topic discussion with a client. The percentages varied
based on the disciplinary background, with social workers having the lowest willingness
to initiate. With only 75 participants derived using convenience sampling, these results
may not be a true reflection of the overall area of practice (Yelton & Delfin, 2015).
Psychologists’ Willingness to Engage Patients
In their study of 110 practicing US and Canadian psychologists (83.6% of whom
were clinically-focused, and 16.4% of whom were counseling-focused), Miller and Byers
(2012) found that sexuality was not often brought up or addressed and older
psychologists were slightly more willing to engage clients about sexuality. Miller and
Byers used Bandura’s theoretical framework for understanding and interpreting the
results based on how self-efficacy impacted the process. They concluded that an increase
in knowledge germane to sexuality and postgraduate sexuality-focused workshops and
other educational opportunities were key to increasing self-efficacy and increasing
willingness to engage patients about sexual topics.
Træen and Schaller (2013) examined the predictive factors for willingness to
discuss sexual issues with their patients in a sample of Norwegian psychologists. Their
data revealed that attitudes and beliefs were the predictive factors after controlling for
age, gender, years of practice, and training in sexology. Older, more experienced
psychologists were more willing to discuss sexual issues. However, one in five reported

48
that they often or always engaged their clients about their sexuality. This result was
similar to Miller and Byers’s (2012) results.
Hanzlik and Gaubatz (2012) focused their study on the comfort of PsyD students
when discussing sexual issues with clients; these participants were not willing to engage
with clients on sexual topics. Furthermore, male clients who saw female therapists may
“…suffer from the tacit minimization or even outright avoidance of their sexual
concerns.” The authors found this concerning since an ever-increasing number of female
psychologists are entering the field (Hanzlik & Gaubatz, 2012, p. 229).
Knowledge
Health Care Professionals’ Knowledge Regarding Sexual Topics
Reflected in the literature was an overall lack of knowledge regarding sexuality
among all involved in health care, therapy and counseling, and psychology. This lack of
knowledge represents a barrier to communication with patients and clients (Bal &
Sahiner, 2015). The following literature is representative of this widespread phenomenon.
In a study of Turkish nurses, Bal and Sahiner (2015) found that lack of sexual
knowledge was a barrier to communication with patients about their sexual issues. Nurses
attitudes were positively impacted regarding communicating with patients about sexual
health concerns with training and knowledge. In Haboubi and Lincoln’s (2003) analysis
of 813 replies from nurses to their survey, they found that previous training in sexuality
was low at 14%, while 86% had no training or little training. Of the respondents who had
undergone training, 53% thought it had improved their knowledge and practice, 27%

49
thought it had just improved knowledge, and 20% thought it had been of no use, which
may be more reflective of the instructors than their opinions regarding training.
In their research, Banwari et al. (2015) used the Attitudes toward Homosexuals
Questionnaire (AHQ) and the Sex Education and Knowledge about Homosexuality
Questionnaire (SEKHQ) and analyzed the results using multiple linear regression. The
results were only applicable to the Indian physicians who participated in their survey, but
the authors noted that these results were in line with American and Canadian knowledge
bases, with a slightly more biased framework concerning homosexuality because of
cultural factors.
Saunamäki et al. (2010) surveyed Swedish registered nurses using the SABS;
90% of those surveyed understood the importance of sexual health and concerns of
patients. However, 60% did not feel confident discussing these topics due to a lack of
competency and knowledge. Saunamäki et al. argued for further education as a means to
increase knowledge for nurses dealing with patients regarding sexual concerns.
Vieira et al. (2015) studied Brazilian OB/GYN residents, 49% of whom had
received no training up to that point regarding sexuality, with 29% reporting having
received 6 hours of training or less. Fifty-six percent never or rarely took a sexual history,
and 51% did not feel competent to do so. The authors concluded that there was an
immediate need for sexually-specific training for medical students and residents.
In research conducted in the southeast US, 38% of medical students had received
no sexuality training (Valvano et al., 2014). Helland et al. (2013) surveyed individuals
working in a variety of disciplines—nurses, physicians, physiotherapists, occupational

50
therapists, social workers, and psychologists—and found that 53% of those surveyed
stated that lack of knowledge was a significant barrier. The professionals who had more
education in sexuality initiated the discussion with patients more often and were more
comfortable in the process. Haesler et al. (2016) studied health care professionals’
attitudes and knowledge toward older patients’ sexuality. These practitioners did not have
sufficient knowledge and considered older patients’ sexual health to be beyond their
scope of practice. In other words, lack of knowledge was a barrier.
Kotronoules et al. (2009) conducted a comprehensive meta-analysis of the
literature, examining 18 studies over three decades regarding oncology nurses and
sexuality. Oncology nurses had positive attitudes, but limited sexual knowledge; this was
a barrier to discussing sexual health issues with patients.
Lapinski et al. (2014) studied attitudes, knowledge, and acceptance of LGBT
patients by 1335 osteopathic medical students using the Klein Sexual Orientation Grid
and the Homosexuality Attitude Scale. The participants reported favorable attitudes and
acceptance levels; these were higher in those who self-identified as LGBT. “Only 125
respondents (12.9%) obtained a passing score” on the section testing medically relevant
knowledge of sexual issues (p. 792). While the LGBT self-identified students’ scores
were higher than their heterosexual peers, the study results suggested that students lacked
adequate knowledge for the competent treatment of sexual health issues for the LGBT
community.
Levesque (2013) conducted a similar study of 416 nurse practitioners with the
variables being self-efficacy, attitudes, and knowledge, but used the Attitudes Toward

51
Transgender Survey and Health Care Provider Survey by Burch (2005) to understand the
nurse practitioners’ perspective. Nurse practitioners lacked both knowledge and self-
efficacy; a result, the authors argued, that impacted their ability to interact with and
engage transgender patients on sexual health issues. Kline (2014) found a similar result
when he surveyed 80 nurse practitioners, 80% of whom agreed they needed more training
to serve the transgender community competently. Riggs and Bartholomaeus (2016)
surveyed Australian mental health nurses using the Attitudes Toward Transgender
Individuals Scale and Counselor Attitude Toward Transgender Scale and found that those
who had undertaken training on transgender health issues had a higher knowledge than
those who had not been trained. The survey results also indicated a correlation between
older age and higher knowledge, as well as between female nurses and higher knowledge.
Although limited by its small sample size (n=96), the study authors believed that it was
generalizable to the larger mental health nursing population, including in the United
States and Canada. In Sidi et al.’s (2013) research involving Malaysian medical students
regarding general sexual health knowledge and attitudes, 73.2% of those surveyed
reported that “they had not received adequate training,” (p. 107) education, and
knowledge regarding how to deal with sexual health issues in the measures used. Fifty-
five percent had adequate sexual health knowledge. Sidi et al. stressed the importance of
integrating sexual health training and education into the core of the medical school
curriculum and noted that integration could achieve more positive attitudes and higher
knowledge while reducing the likelihood that therapists would not overlook patient’
sexual health concerns or leave them unaddressed.

52
There are few studies designed to examine sexual training and its long-term
effects. One of the few was a longitudinal study designed by Fronek et al. (2011) as a
follow-up (2 years later) to a randomized controlled study regarding training for
rehabilitation practitioners working with people who had experienced spinal cord
injuries. The researcher found that training had a long-lasting impact on practitioners’
knowledge, attitudes, and comfort. Fronek et al. noted that the more focused the training
was to the discipline and the individual needs of the practitioners, the more likely the
positive effects would be impactful and lasting.
Using the KCAASS, Verschuren et al. (2013) studied physicians’ knowledge
regarding sexual health issues and how often these issues were addressed for patients
with lower limb amputation. The participants rated their knowledge as almost sufficient,
but the results from the instrument indicated that their knowledge was, in fact,
sufficiently competent. Despite having sufficient knowledge, Verschuren et al. (2013)
still recommended more training specific to sexual knowledge to increase overall sexual
knowledge and to improve the comfort, competency, and willingness of physicians to
engage with patients on sexual topics. West et al. (2012) also encouraged implementation
of curriculum focused on sexual health and related issues for medical students due to the
impact of knowledge on other important variables including attitude, skill, and comfort.
Higgins et al. (2012) conducted a mixed methods study with health care
providers, using a pre-test and post-test survey and interviews after a 1-day training
program had been presented to participants. Data were analyzed using
t-tests. The researchers found marked improvement for health care providers who

53
participated in the program concerning their knowledge, comfort, and skill when
discussing sexual topics with patients.
Strong and Folse (2015) did a similar training intervention designed to improve
undergraduate nursing students’ attitudes and knowledge regarding LGBT patients.
Strong and Folse’s intervention was not about sexual health issues in general, but rather
was focused on the medical needs of transgender patients, including their sexual health
concerns. The Attitudes Toward Lesbians and Gay Men Scale was used, which had high
internal consistency as determined by Cronbach’s alpha, and high reliability (α=.95). The
authors used two other instruments they had developed; the post-test results revealed a
statistically significant increase in knowledge on all 15 items and revealed positive
attitudes toward the LGBT patient community.
In Taiwan, Sung and Lin (2013) used a 12-week-long educational intervention for
a quasi-experimental study using both control and experimental group. Both groups were
comprised of 95 nursing students. The researchers analyzed the longitudinal results from
the pre-tests and post-tests, using the hierarchical linear model. The results of the
intervention were both positive and statistically significant. The results revealed that the
students in the experimental group showed significant improvements over those in the
control group on knowledge (β=−0.27, P<0.001), attitude (β=−0.38, P<0.001), and self-
efficacy (β=−0.90, P<0.001)” (p. 498).
Tugut and Golbasi (2015) designed an educational intervention—a total of 18
hours presented over 3 days—to the experimental group of Turkish nursing students.
Participant assignment to the experimental group or the control group was randomized.

54
The researchers assessed the students’ attitudes, knowledge, and skill by using the
“Sexuality Assessment Information Test, Sexual Attitude and Beliefs Scale, and
Sexuality Assessment Skills Check List” (p. 1). After the intervention, the scores of “the
experimental group [were] significantly higher than mean scores of students in the
control group (p < .05)” (p. 1). Tugut and Golbasi highlighted the importance sexual
health was to a complete understanding of how to interact with and assess patients’ needs
and to engage in a holistic practice of medicine. The educational component regarding
sexual health was found lacking. The nursing students did not have the necessary
informational base upon which to rely when engaging with patients. This, in turn, formed
a barrier, which with proper training, was overcome.
Simpson, Anwar, Wilson, and Bertapelle (2006) found marked improvement after
training staff members who worked with patients having neurological disabilities. In this
experimental study (with control and experimental groups), Simpson et al. used the
Sexual Attitude Scale, the Role Skills Intervention Survey, a single item for comfort, and
an author-designed knowledge assessment. The experimental group and control group
had similar pretest scores but significantly different posttest scores; the gains from the
experimental group were also found six months later. The staff who had been in the
experimental group were found to engage patients more often about sexual health issues
and were more knowledgeable.
Similar positive results were not observed among Tennessee physicians from two
hospitals in a study designed to determine the impact of training and mandatory protocols
regarding anti-discrimination for the sexual and gender minority community (SGM)

55
(Jabson et al., 2016). Although one hospital had implemented these protocols and
training, there was no significant difference in knowledge or treatment of SGM patients
found between the physicians who had taken the training and those who did not. The
authors recommended more research into affirmative practices that might help the SGM
community to discover a more effective way to minimize or eliminate discrimination
against SGM patients.
Counselors’ and Therapists’ Knowledge Regarding Sexual Topics
Harris and Hays’s (2008) research into the willingness of marriage and family
therapists to engage their clients as impacted by the variables of sexuality knowledge and
comfort was a seminal article on this topic and is the most often cited resource. The
authors found that sexuality knowledge and supervision, with training specific to
sexuality, influenced the willingness of therapists to engage their clients. While Harris
and Hays’s (2008) findings conflicted with Decker (2010) regarding how knowledge
impacted comfort, both Decker, Harris, and Hays agreed that supervision was a
cornerstone upon which the foundation of a great therapist, willing to engage and discuss
sexual health issues with patients, was laid. Harris and Hays highlighted the importance
of graduate-level sexuality education and training because it impacted the comfort and
willingness of therapists to interact with clients and decreased the anxiety inherent in
discussing this topic. Harris and Hays used the Bowenian theoretical framework for their
research on this topic; the only study to do so.
Decker (2010) focused her dissertation on supervisors and how they addressed the
needs of clients regarding sexuality; the supervisors had sufficient knowledge in nine of

56
15 areas regarding the sexual health needs of clients. Decker found that over 70% of
supervisors recommended trainees include sexuality as a consideration and 50%
recommended that trainees take a sexual history of their clients. The supervisors who had
sought out graduate courses or postgraduation training in sexuality areas reported having
more knowledge. However, a correlation between knowledge and comfort was not found,
conflicting with other studies, including Harris and Hays (2008), who did find a
correlation between knowledge and comfort. Decker noted the dearth of research in this
area, which prompted her to create the survey instrument she used in her research.
In contrast, Kazukauskas and Lam (2010) found a correlation between comfort
and knowledge among their certified rehabilitation counselor participants; as knowledge
increased, comfort increased as well. While participant data showed average knowledge,
there was also a need for further education to increase competency, decrease approach
anxiety, and improve the quality of care.
Pebdani (2013) conducted a similar study regarding rehabilitation master’s
program students using the same instruments as Kazukauskas and Lam (2010) and found
that training had a significant impact on knowledge regarding sexual needs of patients
who were going through rehabilitation. Pebdani noted that these findings were consistent
with the prior research and that training focused on sexuality improved sexual knowledge
of the counselors who then, as demonstrated by Juergens et al. (2009), were more willing
to engage patients and were more comfortable in the process.
Farmer et al. (2013) studied 468 school and community counselors’ competency
with LGB knowledge and attitudes. Participants’ requisite knowledge was lacking

57
regarding how to interact with and address the needs of this population. School
counselors were shown to have lower scores than their community colleagues in this area.
Farmer et al. noted that these findings were consistent with previous research where there
was a general lack of knowledge.
In a meta-analysis of marriage and family therapists, Dermer and Bachenberg
(2015) addressed the fact that no significant advancement by marriage and family
therapists has been made regarding treatment of clients’ sexual health needs and
concerns; neither has therapists’ comfort in discussing sexuality with clients.
Furthermore, there has not been a call to change the educational structure so these skills
and knowledge can be acquired.
Psychologists’ Knowledge Regarding Sexual Topics
There is also a lack of literature on the topic under discussion in the field of
psychology. Several of the following studies were conducted in other disciplines but
included psychologists as participants.
Flaget-Greener et al. (2015) conducted a survey of “119 doctoral-level
psychologists licensed in the US, who reported to be the members of the American
Psychological Association (APA)” (p. 13) to discover whether education, training,
sociodemographic characteristics, and attitudes had any impact on their willingness to
engage clients in sexual topics. Flaget-Greener et al. did not find a link or correlation
between education and attitude toward treating older individuals’ sexual health concerns.
The authors noted that this might have been due to the homogeneity of the participants:
Permissive attitudes tend to correlate with higher education. Flaget-Greener et al. found

58
“that attitudes toward older adults’ sexuality and sexual education and training were
predictive of psychologists’ willingness to assess older adults’ sexual health, despite
participants’ demographic characteristics” (p. 19). They concluded that a key component
in increasing psychologists’ willingness to engage is to increase training specific to
sexuality and sexuality education, along with changing attitudes.
In a study of 384 Veterans Administration psychologists, participants completed a
survey regarding their attitudes and knowledge, needs and interests in training, self-
reported competence, current practice, experience, and training regarding LGBT patients
(Johnson & Federman, 2014). Data indicated that 83.6% had attended one course or less
regarding transgender issues; 55.8% had one class period or less on sexual orientation
issues. Over 55% did not ask questions about sexual orientation to aid their treatment
options, 92% did not ask about gender identity. Johnson and Federman (2014) noted the
significant relationship between training specific to LGBT issues in graduate school and
the long-term positive effects this training had on attitudes and experience. These results
underscore the importance of knowledge acquisition.
Valvano et al. (2014) found that psychology students received the least amount of
classroom hours focused on sexuality when compared to the other allied health
disciplines: 69% received no sexuality education on how to interact with clients about
their sexuality. This was compared to 9% of nurses who had not received a similar
education. The authors also found that medical students had the highest number of direct
contact with patients (only 38% had no hours of direct contact) regarding sexual health
issues, while psychology students had the least (94% had no hours of direct contact).

59
Psychology students seemed to be aware of this by rating their quality of education
regarding sexuality significantly lower (M = 2.06, SD = 1.01) than their medical student
peers (p < 0.01 for all comparisons). Valvano et al. also noted that students not only
lacked sufficient quantity, but the quality of sexuality education was also lacking. The
authors argued that this lack resulted in psychologists who were ill-equipped to handle
such discussions and would not be confident in their ability to do so. Valvano et al. urged
that curriculum devoted to sexuality, sexual health, and direct contact with clients be
integrated into the educational paradigm. Their conclusion was consistent with Decker’s
(2010). Despite the fact that Decker was examining counselors in her study, it would
seem appropriate to consider her conclusions in light of Valvano et al.’s
recommendations.
Summary and Conclusions
In summary, the literature pointed out that marriage and family therapists are not
meeting the needs of their clients, that this need is pressing, and that failure to meet the
need could cause damage (Cupit, 2010; Harris & Hays, 2008; Juergens et al., 2009;
LoFrisco, 2013; Papaharitou et al., 2008; Timm, 2009). This is not a unique problem to
the marriage and family therapy profession because a wide variety of health care and
medical professions are currently dealing with similar problems of failing to engage and
address sexual health issues (Helland et al., 2013; Kotronoulas et al., 2009; Verschuren et
al., 2013; Vieira et al., 2015)
In conclusion, no studies were found that included the independent variables of
knowledge and attitude to determine the effect on the dependent variables of comfort and

60
willingness to engage clients in sexual discussions for marriage and family therapists.
Furthermore, no researchers used the instruments in the manner I proposed: to determine
what impact, if any, knowledge and attitude have on comfort and willingness to engage
clients about their sexual lives and experiences by the marriage and family therapists
surveyed. The need for this study is further strengthened by the lack of studies in this area
(Cupit, 2010; Decker, 2010; Harris & Hays, 2008; LoFrisco, 2013; Miller & Byers, 2012;
Yelton & Delfin, 2015). The methodology chosen for this study, which follows similar
design and method choices of Cupit (2010) and Harris and Hays (2008), is discussed in
Chapter 3.

61
Chapter 3: Methodology
The purpose of this study was to examine the variables that affect marriage and
family therapists’ willingness and comfort to engage in and discuss the topic of sexuality
with clients to whom they provide therapy. The overarching research question was the
following: How can therapists’ increase their levels of comfort and their willingness-to-
engage so clients’ care does not suffer and therapy is a positive experience conducted in a
protective environment? The two dependent variables investigated were (a) therapists’
comfort in discussing sexual topics, and (b) therapists’ willingness to engage and discuss
sexuality with clients. The independent variables that were measured were therapists’ (a)
attitudes, (b) knowledge, (c) training, (d) supervision experience, (e) clinical experience,
(f) sex, (g) age, (h) strength of religion, (i) sexual orientation, (j) practice experience, (k)
practice setting, (l) graduate specialization, and (m) relationship status.
This study was quantitative and correlational and was derived from the methods
from Cohen, Manion, and Morrison (2007). I consulted Bowen and Kerr (1988) for
guidance regarding the use of Bowenian theory, and Harris and Hays (2008) for how I
should treat the variables within a Bowenian framework.
In Chapter 3, I explain why the correlational design was appropriate and describe
the study instruments. I also provide the rationale, population, sample size, and sampling
procedures for the study. Next, I provide information on data collection, measurement
instruments, operationalization of variables, data analysis, and threats to validity. Finally,
I address ethical issues and procedures used to mitigate any concerns.

62
Research Design and Rationale
The purpose of this study was to examine how the independent variables of sexual
knowledge, training, supervision, clinical experience, and personal sexual attitudes of
therapists influence their comfort and willingness to engage in and discuss the topic of
sexuality with a client. The study purpose dictated the research methodology and the
associated design that I used (see Conrad & Serlin, 2005; Edmondson & McManus,
2007). Harris and Hays (2008) and Cupit (2010) used quantitative methodology for
similar research. I designed the current study to determine the specific factors that
influence a particular outcome and to identify the best predictors of therapists’
willingness to engage in topics of sexuality and therapists’ comfort discussing sexuality
with clients. I considered a quantitative approach as best suited for the study’s purpose
(see Creswell, 2009).
A qualitative approach was not suitable for this study because the issue of
therapists not being comfortable and not being willing to discuss sexual issues with
clients was not new (see Harris & Hays, 2008). The variables necessary to examine the
relationships between sexual knowledge, training, supervision, clinical experience, sexual
attitudes, sexual comfort, and willingness to engage and discuss sexual topics were well
known and did not require an exploratory approach (see Creswell, 2009). Because these
variables were known, I could measure the predictive relationships among them.
I used a cross-sectional correlational survey design because this design lends itself
to research and analyzing predictive relationships among variables (see Creswell, 2009).
This type of survey design was appropriate for identifying correlations (see Marczyk,

63
DeMatteo, & Festinger, 2005; Monette, Sullivan, & DeJong, 2007). The cross-sectional
survey design is the typical choice for this type of research, requiring less time to finish
and fewer resources (see Carlson & Morrison, 2009; Polit & Beck, 2006). The survey
design is also an appropriate choice when standardized instruments are used for data
collection from a large number of participants who live in different geographical areas
(see Creswell, 2009; Kothari, 2004). The cross-sectional design allows for the generation
of a hypothesis from the variables assessed, which allows for the addition of knowledge
to the topic area and for further research (see Carlson & Morrison, 2009).
I did not add a longitudinal dimension to this study because of the lengthy follow-
up process that would have been required, as well as the cost associated with such a study
(see Aschengrau & Seage, 2008). One of the benefits of the chosen design was there were
no issues from participants dropping out that could have skewed the results (see
Aschengrau & Seage, 2008). Although this design did not allow for causation to be
established among the variables and the survey approach may have resulted in low
internal validity, the design allowed for precise findings that yielded answers to the
research questions (see Creswell, 2009; Frankfort-Nachmias & Nachmias, 2008; Szklo &
Nieto, 2014).
Population
The population from which I drew the participants were state-licensed, active,
marriage and family therapists who provided therapy to clients. Participants were actively
engaged in therapy with clients and were not engaged in other types of employment, such
as teaching. This population was finite: There are 32,070 marriage and family therapists

64
practicing in the United States, according to the most recent Bureau of Labor Statistics
from May 2016 (U.S. Department of Labor, Bureau of Labor Statistics , 2017).
Sampling and Sampling Procedures
I used random sampling in this study (see Frankfort-Nachmias & Nachmias,
2008). Simple random sampling is a probability-based sample design that I used to ensure
every U.S. marriage and family therapist had “an equal and nonzero probability in being
selected” (see Frankfort-Nachmias & Nachmias, 2008, p. 169). I drew the sample from a
list of marriage and family therapists practicing in the United States, who were licensed
in their state, who possessed a master’s or doctoral degree, and who were active in their
profession. This list was available for purchase online.
Determining the sample size necessary to provide accurate results was based on
three factors. The first was the power of statistical analysis (see Kuehl, 2000). The second
was effect size, which measured the relationship between the independent and dependent
variables and the magnitude that resulted. Level of significance was the third factor that
impacted the sample size. I used G*Power to determine the necessary minimum sample
size based on a level of significance. I used a high power of 0.95, a medium effect size
equal to f2 = 0.15, and a significance level of 0.5. The total number of predictors was two,
and I used a 95% confidence level with a confidence interval of ±5%. Given these
parameters, the minimum sample size was 107 as computed with G*Power using the F
test for multiple linear regression with the fixed model and R2 deviation from zero.
A type II error (Merriam-Webster, n.d.) can occur when doing statistical analysis
(Frankfort-Nachmias & Nachmias, 2008). To guard against this failure to reject a false

65
null hypothesis, which can be attributed to inadequate sample size, I included at least 110
participants in the analysis (see Frankfort-Nachmias & Nachmias, 2008). Therefore, at
least 110 marriage and family therapists had to complete and return the surveys. I chose
the participants at random from the email lists, and I expected about 10-15% to be
returned based on previous literature. To achieve this goal of 110 surveys completed by
marriage and family therapists, I emailed the survey to 2,000 marriage and family
therapists to meet the minimum sample size, as computed by G*Power, necessary to
reduce the chances of a type II error occurring during the statistical analysis.
Procedures
Survey Monkey is an online service available free of charge that I used to design
and create the survey for this research. I composed an e-mail invitation to potential
participants, e-mailed the survey link to those who accepted the invitation, and collected
the responses. Step 1 in this process was to convert the existing instruments into the
Survey Monkey’s questionnaire format. Step 2 was to compose an e-mail explaining the
study and send the email to 2000 potential participants to solicit their participation. The
survey explanation included an outline detailing the purpose of the study and how I
would maintain anonymity. I required informed consent from each participant before
starting the survey; the participants affirmed their voluntary participation and
understanding that they were free to quit at any time if they felt uncomfortable or
otherwise compromised before gaining access to the survey. I did not use follow-up
procedures in this study. I tracked the results on Survey Monkey, verified the data to

66
ensure no corruption or errors occurred in its transmission (Step 3), and analyzed the data
using Statistical Package for the Social Sciences (SPSS) 24 (Step 4).
Instrumentation and Operationalization of Constructs
Demographic Data
Cupit (2010) developed the demographic data instruments that I used in this
study. The author used this instrument when studying “counselors who were members of
the American Counseling Association” (p. 13). The variables measured by this instrument
were sex, age, strength of religion, sexual orientation, practice experience, practice
setting, graduate specialization, and relationship status. Published reliability and validity
values were not relevant because I used this instrument to collect demographic
information about the participants.
24-Item Miller-Fisk Sexual Knowledge Questionnaire
Warren Miller and Norman Fisk developed the original 49-item Miller-Fisk
Sexual Knowledge Questionnaire in 1969, consisting of questions related to sex drive,
fertility, reproduction, contraception, and menstruation (Gough, 1974). I used a shortened
version of this instrument, the 24-Item Miller Fisk Sexual Knowledge Questionnaire, in
the current study. The questions on this instrument were either true/false or multiple
choice with four options. I based the total score on the correct number of answers, and a
high score indicated sexual knowledge. An example item was “Withdrawal is an effective
means of contraception (birth control)” with a true/false answer.
This shortened version was tested for validity in a study that involved 209 male
participants and 146 female participants in Sample 1, and 78 male participants and 100

67
female participants in Sample 2 (Gough, 1974). Statistical significance was found at
every point-biserial coefficient when measured in the .01 level; internal consistency was
found to be sufficient (Gough, 1974). In follow-up research, 355 students were tested for
odd-even reliability coefficients; the corrected coefficients were found to be .62 for
female participants, .70 for male participants, and .67 overall (Gough, 1974). The mean
for the male participants was 15.51, with an SD = 3.77; the mean for the female
participants was 16.55, with an SD = 3.47 (Gough, 1974). The overall mean was 15.94
with an SD = 3.69 (Gough, 1974). The 1.04 difference between the two sexes gave a t
ratio of 2.68, p ≤ .01 (Gough, 1974). Cupit (2010) subsequently used this instrument as
did Russell, Gates, and Viggiani (2016) in the most recent research on mental health
counselors’ attitudes and knowledge toward sexual health issues.
Sexual Comfort Scale
Harris and Hays (2008) developed the Sexual Comfort Scale and used it in their
initial study using a 7-point Likert-type scale (1 = uncomfortable; 7 = comfortable) to
measure how comfortable a therapist would be discussing sexual topics with clients. An
example item was “I respond openly and confidently when my sexual values are
challenged.” The Sexual Comfort Scale was appropriate for this study because I aimed to
survey marriage and family therapists using the same variables as those used by Harris
and Hayes (2008); my research was an extension of their work. Harris and Hays (2008)
found the Cronbach’s alpha at 0.86 but there was no validity or reliability data beyond
that for this instrument.

68
Brief Sexual Attitudes Scale
Hendrick, Hendrick, and Reich (2006) developed the Brief Sexual Attitudes Scale
(BSAS), which was an update to the authors’ previous scale, the Sexual Attitudes Scale
(SAS). The BSAS was appropriate for this study because several researchers had used it
to measure the sexual comfort of mental health professionals (see Cupit, 2012; Hanzlik &
Gaubatz, 2012). The subscales of the BSAS include birth control, permissiveness,
instrumentality, and communion.
Hendrick et al. (2006) designed the BSAS with a 5-point, Likert-type scale from 1
= strongly agree to 5 = strongly disagree. Low scores indicated permissive sexual
attitudes. Example items were “I would like to have sex with many partners” or “Casual
sex is permissible.” I used this scale to measure sexual attitudes of the marriage and
family therapists in the current study.
Hendrick et al. (2006) used three different samples to measure the reliability and
validity of the BSAS. The authors drew the first sample from 674 undergraduates from a
university in the southwestern portion of the United States, and the resulting four
subscales’ alphas were birth control = 0.84, permissiveness = 0.93, instrumentality =
0.77, and communion = 0.71. This was consistent with previous alphas from the original
SAS. The BSAS “performed similarly to the original scale (and consistently with
previous research) when correlated with the other scales” (Hendrick et al., 2006, p. 81).
Hendrick et al.’s (2006) second study included 528 participants enrolled at the
same university who were in a psychology course. Hendrick et al. compared the SAS
with the BSAS and found a 0.98 on a goodness of fit index. The chi-square test indicated

69
that the difference between the scales was highly significant (p < 0.001). The alphas for
the subscale were birth control = 0.87, permissiveness = 0.95, instrumentality = 0.80, and
communion = 0.79; the correlations drawn from the BSAS were comparable to the SAS.
Hendrick et al.’s (2006) third and final study also drew participants from the same
university and they also selected 518 participants from psychology students who were in
the introductory phase. The test–retest reliability was found 0.20 or lower when
measured. The alphas were birth control = 0.88, permissiveness = 0.95, instrumentality =
0.77, and communion = 0.73 with the retest as follows: birth control = 0.57,
permissiveness = 0.92, instrumentality = 0.75, and communion = 0.86. The subscales
included 10 items for permissiveness, three items for birth control, five items for
communion, and instrumentality with five items.
Sexuality Education Scale
Harris and Hays (2008) developed the Sexuality Education Scale, which consists
of seven items. For example, Harris and Hays and Cupit (2010) both used this scale in
their research with marriage and family therapists and counselors respectively regarding
the variables in this study. “There are no reliability or validity data on this scale” (Cupit,
2010, p. 72). However, Harris and Hays found it suitable (Cupit, 2010).
Experience in Supervision Scale
The Experience in Supervision Scale was developed to measure the number of
interactions therapists had while being supervised that involved discussions of sexuality
(Harris & Hays, 2008). Cupit (2010) and Harris and Hays (2008) also used this
instrument in their studies of marriage and family therapists and counselors respectively

70
regarding the variables in the current study. “There is no reliability or validity data for
this scale” (Cupit, p. 73).
Clinical Experience Scale
Harris and Hays (2008) created the Clinical Experience Scale to assess the
aggregate experience therapists had in clinical settings discussing sexual issues. Cupit
(2010) and Harris and Hays also used this instrument in their studies of marriage and
family therapists and counselors respectively regarding the variables in the current study.
“There is no reliability or validity data for this scale” (Cupit, p. 73).
Sexuality Discussion With Clients Scale
Harris and Hays (2008) developed the Sexuality Discussion with Clients Scale to
assess the willingness of therapists to engage in discussions with clients about sexual
topics. It was appropriate for this study because Harris and Hays and Cupit (2010) had
used it in their study of marriage and family therapists and counselors respectively
regarding the variables I am examining. Cronbach’s alpha was 0.90 in Harris and Hays’s
study; there was no other data regarding the validity or reliability of this instrument.
Operationalization
I measured sexual knowledge using the 24-item Miller-Fisk Sexual Knowledge
Questionnaire (see Gough, 1974). The participants answered the questions as true/false or
multiple-choice with four options. I based the total score on the correct number of
answers where a high score indicates sexual knowledge. An example item is “Withdrawal
is an effective means of contraception (birth control)” with a true/false answer.

71
I measured sexual attitudes using the BSAS, which is a Likert-type scale
consisting of a 5-point spectrum (see Hendrick et al., 2006). Participants indicated the
extent of their agreement or disagreement on this sliding scale. A lower score indicated a
permissive attitude toward sexuality from 1 = (strongly agree) to 5 = (strongly disagree).
An example item statement is “I would like to have sex with many partners” or “Casual
sex is permissible.” I used this scale to measure marriage and family therapists’ sexual
knowledge.
I measured sexual comfort using the Sexual Comfort Scale (SCS) (see Harris and
Hays, 2008). Hays (2002) developed it by using a 7-point Likert-type scale to measure
how comfortable a therapist would be discussing particular topics with clients. An
example item is “I respond openly and confidently when my sexual values are
challenged” with a scale of 1 = (uncomfortable) to 7 = (comfortable). The higher the
score, the more likely the therapist would be comfortable with discussing sexual issues
with clients. I used this scale to measure marriage and family therapists’ sexual comfort
as it related to the therapy setting.
The Sexuality Education and Supervision Scale is a mix of multiple choice, using
a 7-point Likert-type scale with single answer questions, i.e., what is your gender?
(Harris & Hays, 2008). The instrument assigns one point “for each indication of
participation in sexuality education venue” (Harris & Hays, p. 243). The instrument
consists of 12 items; seven focused on education and five focused on supervision. Higher
scores indicate significant experience levels in discussing sexual topics with clients. I

72
used this scale to measure the marriage and family therapists’ sexual educational
background and supervision experience.
The Clinical Experience Scale is an instrument comprised of five items with a
multiple-choice format, and “…higher scores indicate more clinical experience” (Harris
& Hays, 2008, p. 243). An example item is “Clinical experience with sexual issues” with
a multiple-choice answer portion with answer options such as “I have clinical experience
with only one or two cases involving sexuality issues.” I used this scale to measure
marriage and family therapists’ clinical experience. The last scale from Harris and Hays
(2008) is the Sexuality Discussion with Clients Scale. This scale is comprised of nine
items that measure on a 7-point Likert-type scale. A higher score indicates that a marriage
and family therapist has an increased willingness to initiate a sexual discussion with a
client. I used this scale to measure marriage and family therapists’ willingness to discuss
sexual issues with clients. I examined the independent variables of sex, age, strength of
religion, sexual orientation, practice experience, practice setting, graduate specialization,
and relationship status using the Demographic Data instrument (see Cupit, 2010).
Data Analysis Plan
The data analysis software I employed in this research was SPSS 24.0. I ran a
frequency analysis to ensure I had correctly entered the data and there were no missing
values due to answers omitted by participants. I also eliminated missing data as needed.
Thereafter, I analyzed the data using a similar approach to that of Harris and Hays (2008)
and Cupit (2010), which included using “descriptive statistics, correlation, comparative,
and multiple regression analysis using stepwise linear regression” (see Cupit, p. 76). I

73
used stepwise linear regression to determine which of the following independent
variables, attitudes, knowledge, training, supervision experience, and clinical experience,
or which combination of those independent variables, attitudes, knowledge, training,
supervision experience, and clinical experience, had the greatest statistical significance
when acting upon the dependent variable of a therapist’s comfort level with sexuality.
The BSAS measured the independent variables for attitudes, the Miller-Fisk Sexual
Knowledge Questionnaire for knowledge, sexuality education and Supervision Scale for
training and supervision, and the Clinical Experience Scale for clinical experience. The
variables of attitudes and knowledge were ordinal because I measured them on a 7-point
Likert-type scales. The variables of training, supervision experience, and clinical
experience were nominal because I measured them by items that if checked, increased the
score, i.e., the more items checked, the higher the score. I measured the dependent
variable of the therapist’s comfort level with sexuality by using the Sexual Comfort
Scale, which is also a 7-point Likert-type scale; the variable was ordinal.
I also used stepwise linear regression to determine which independent variables
(attitudes, knowledge, training, supervision experience, and clinical experience) or which
combination of independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) had the greatest statistical significance when acting
upon the dependent variable of a therapist’s willingness to discuss sexual topics with
clients. The BSAS measured the independent variables for attitudes, the Miller-Fisk
Sexual Knowledge Questionnaire for Knowledge, Sexuality Education and Supervision
Scale for training and supervision, and the Clinical Experience Scale for clinical

74
experience; the variables of attitudes and knowledge were ordinal because I measured
them on 7-point Likert-type scales. The variables of training, supervision experience, and
clinical experience were nominal since I measured them by items that, if checked,
increased the score, i.e., the more items checked, the higher the score. The Sexuality
Discussion measured the dependent variable of the therapist’s willingness to discuss
sexual topics with the Sexuality Discussion with Clients Scale; this scale is also a 7-point
Likert-type scale, and the variable was ordinal. Stepwise linear regression was an
appropriate statistical test and provided a statistical analysis method wherein I used both
nominal and ordinal variables in the same test to analyze their impact on the dependent
variable.
Research Questions and Hypotheses
I used the following research questions (RQs) and hypotheses to guide the study:
RQ1: What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s willingness to discuss sexual topics
with clients?
H01: There is no statistically significant relationship between attitudes,
knowledge, training, supervision experience, and clinical experience and a therapist’s
willingness to discuss sexual topics with clients.
Ha1: There is a statistically significant relationship between attitudes, knowledge,
training, supervision experience, and clinical experience and a therapist’s willingness to
discuss sexual topics with clients.

75
RQ2: What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s comfort discussing sexual topics
with clients?
H02: There is no statistically significant relationship between attitudes,
knowledge, training, supervision experience, and clinical experience and a therapist’s
comfort discussing sexual topics with clients.
Ha2: There is a statistically significant relationship between attitudes, knowledge,
training, supervision experience, and clinical experience and a therapist’s comfort
discussing sexual topics with clients.
RQ3: What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s comfort level with sexuality?
H03: There is no statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort level with sexuality.
Ha3: There is a statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort level with sexuality.
RQ4: What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s willingness to discuss sexual
topics with clients?

76
H04: There is no statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to discuss sexual topics with clients.
Ha4: There is a statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to discuss sexual topics with clients.
RQ5: What is the relationship between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of
the sexual comfort of a therapist?
H05: There is no statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of the sexual comfort of a therapist.
Ha5: There is a statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of the sexual comfort of a therapist.
RQ6: What is the relationship between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of a
therapist’s willingness to discuss sexual topics?

77
H06: There is no statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to discuss sexual topics?
Ha6: There is a statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to discuss sexual topics.
Data Analysis for Hypothesis 1: A Pearson-product moment correlation will be
conducted for each independent variable.
Data Analysis for Hypothesis 2: A Pearson-product moment correlation will be
conducted for each independent variable.
Data Analysis for Hypothesis 3: A stepwise linear regression will be conducted to
determine whether one or more of the variables can adequately predict a therapist’s
sexual comfort when discussing sexual topics.
Data Analysis for Hypothesis 4: A stepwise linear regression will be conducted to
determine whether one or more of the variables can adequately predict a therapist’s
willingness to discuss sexual topics with clients.
Data Analysis for Hypothesis 5: A Pearson-product moment correlation will be
conducted for each independent variable, those being therapist’s age, sex, sexual
orientation, number of years in practice, type of graduate program, relationship status,
practice setting, and strength of religion, and a Chi-square measure of assessment will be

78
used to determine the scores compared with the dependent variable of a therapist’s sexual
comfort.
Data Analysis for Hypothesis 6: A Pearson-product moment correlation will be
conducted for each independent variable, those being therapist’s age, sex, sexual
orientation, number of years in practice, type of graduate program, relationship status,
practice setting, and strength of religion, and a Chi-square measure of assessment will be
used to determine the scores compared with the dependent variable of a therapist’s
willingness to discuss sexual topics with a client.
I used correlation, descriptive statistics, comparative, and multiple regression
analysis using stepwise linear regression. Stepwise linear regression allowed me to sort
through each independent variable to determine which independent variable or which
combination of independent variables had the greatest statistical significance when acting
upon the dependent variable.
Threats to External and Internal Validity
Campbell and Stanley (1966) identified four threats to external validity:
interaction between the test subjects and the treatment, pretesting, setting interaction
issues, and multiple treatments causing issues. Creswell (2009) identified three types of
threats to external validity: interaction of selection and treatment, the interaction of
setting and treatment, and interaction of history and treatment. Randomization was the
best measure to ensure external validity: I used randomization in this study, therefore,
external validity was high (see Campbell & Stanley, 1966).

79
Threats to internal validity were history, maturation, regression, selection,
mortality, diffusion of treatment, compensation/resentful demoralization, compensatory
rivalry, testing, and instrumentation (see Creswell, 2009). As this study used a
correlational research design using a randomized sample, history maturation, regression,
and selection did not pose a threat to internal validity. Mortality posed a small but
unlikely threat given that most participants finished their surveys once started and
diffusion of treatment was not applicable to this study nor was compensatory/resentful
demoralization or compensatory rivalry. Testing was not an issue because this was only a
one-time questionnaire and instrumentation did not change (see Creswell, 2009).
Threats to Statistical Validity
To perform a linear regression test correctly, several assumptions were met to
provide accurate forecasts, confidence intervals, and insights. If these assumptions had
not been met, then the forecasts, confidence intervals, and insights might have been
misleading or biased. The assumptions underlying a multiple linear regression were the
following: normality, homoscedasticity, linearity, independence of observations, no
multicollinearity, and no significant outliers.
Normality
To ensure that normality was present, the residuals (errors) needed to be
approximately and normally distributed. Two common ways to check this were a
histogram and a normal P-P Plot or a normal Q-Q Plot of the residuals (see Green &
Salkind, 2014).

80
Homoscedasticity
The data needed to demonstrate that there was homoscedasticity present (i.e., the
variances along the line of best fit remain similar when examined through plotting) (see
Green & Salkind, 2014). I avoided heteroscedasticity and examined it by plotting a graph
with the data to determine whether or not homoscedasticity was present. If it was, then
homoscedasticity was present, and the assumption had been met (see Field, 2013)
Independence of Observations
Field (2013) stated independence of observations could be checked by using the
Durbin-Watson statistical test for serial correlations between errors in regression models.
“Specifically, it tests whether adjacent residuals are correlated” (p. 874) to determine the
assumption of independence of errors, with a test that varies between 0 and 4. A value of
2 indicates the residuals are uncorrelated. A value above 2 indicates a negative
correlation, and a value below 2 indicates a positive correlation. If the value is below 1 or
above 3, there is cause for concern.
Linearity
The outcome variable should linearly relate to any predictor variable. This
assumption can be tested by plotting the points on a graph. There should be symmetrical
distribution along a diagonal line in the graph indicating that there is a linear relationship.
However, a bowed or other strange pattern on the graph is indicative of errors (see Field,
2013).

81
Multicollinearity
Field (2013) noted that multicollinearity exists when two or more independent
variables are “closely linearly related” (p. 879), making it difficult to understand which
variable has contributed to the variance in the dependent variable. As collinearity
increases, standard errors increase as well. Also, it limits the size of R. SPSS provides
collinearity diagnostic tests, such as the variance of inflation factor (VIF) to indicate
whether an independent variable has a strong linear relationship with another independent
variable. According to Bowerman and O’Connell (as cited in Field, 2013), “if the largest
VIF is greater than ten then there is cause for concern. If the average VIF is substantially
greater than one, then the regression may be biased” (Field, 2013, p. 325). Similarly,
Menard (determined that a “tolerance below 0.1 indicates a serious problem [and]
tolerance below 0.2 indicates a potential problem (as cited in Field, 2013, p. 325).
Outliers
Outliers are observations that are significantly different from the majority and
lead to standard errors and bias (Field, 2013). SPSS provides statistical tests to ascertain
if outliers exist in data, including the use of a histogram. SPSS also provides a test for
multivariate outliers called the Mahalanobis distance test. For example, if a study with
three predictors, where N = 100, achieves a value of 15 or more, it would be problematic
and would indicate that an outlier is present in the dataset and will require removal before
running a regression analysis (Field, 2013).

82
Ethical Procedures
The participants in this study were volunteers who completed an informed
consent package at the beginning of the survey to ensure they understood the following:
their answers would be confidential, their participation was voluntary, and they could
stop at any time they were uncomfortable or otherwise wanted to stop. I delivered the
informed consent package electronically as the initial portion of the survey. Once
completed, the participants then continued to begin the survey. I informed the prospective
survey participants that by completing the survey, they were acknowledging the potential
risks and understood them. Also, they acknowledged they understood their answers were
being submitted anonymously and that by completing the survey they had given their
implied informed consent. If a participant failed to complete the survey, I discarded the
survey. If I did not reach the necessary number of participants, then I would randomly
choose another set of prospective participants and would email them an informed consent
form and the survey link until I reached the requisite number of survey responses.
In the cover letter that accompanied the survey, bold black letters advised the
prospective participants that their involvement was voluntary. Participants’ answers were
anonymous, so there was limited risk to participants’ confidentiality. I also advised them
not to indicate their identity anywhere in the survey questionnaire.
I conducted this study according to Walden University’s Institutional Review
Board’s requirements relating to human subjects, including ensuring that the participants’
identities remained confidential and that their answers remained anonymous and
untraceable to the participant. I acquired formal permission from Walden University’s

83
IRB before the commencement of the research process with the formal approval issued
under number 07-21-17-0316271.
Summary
In Chapter 3, I outlined the quantitative cross-sectional correlational research
design, the justification for using this design, and the methods that I used to acquire
participant data using Survey Monkey. I also presented descriptions of the participant
sample, eligibility requirements, and the sampling procedures that I used. Participants
provided their informed consent, then answered questions from several instruments.
Next, I analyzed the data to determine if there was any statistically significant
correlational links between the variables in the study. I presented the steps I took to
ensure the ethical standards related to human subjects as defined by Walden University.
Finally, I discussed internal, external, and statistical validity.

84
Chapter 4: Results
The primary purpose of this study was to examine the relationships between the
independent variables of therapists’ attitudes and knowledge and the dependent variables
of therapists’ comfort with sexual topics and willingness to discuss sexual topics. A
secondary purpose of this study was to examine the relationships between the
independent variables of personal characteristics of therapists and the dependent variables
of therapists’ comfort with sexual topics and willingness to discuss sexual topics. A better
understanding of the relationships between these variables in the context of Bowenian
theory provided a significant addition to the body of research in this area.
Research Questions and Hypothesis Testing
I used six research questions and related hypotheses to guide the study:
RQ1: What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s willingness to discuss sexual topics
with clients?
H01: There is no statistically significant relationship between attitudes,
knowledge, training, supervision experience, and clinical experience and a therapist’s
willingness to discuss sexual topics with clients.
Ha1: There is a statistically significant relationship between attitudes, knowledge,
training, supervision experience, and clinical experience and a therapist’s willingness to
discuss sexual topics with clients.

85
RQ2: What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s comfort discussing sexual topics
with clients?
H02: There is no statistically significant relationship between attitudes,
knowledge, training, supervision experience, and clinical experience and a therapist’s
comfort discussing sexual topics with clients.
Ha2: There is a statistically significant relationship between attitudes, knowledge,
training, supervision experience, and clinical experience and a therapist’s comfort
discussing sexual topics with clients.
RQ3: What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s comfort level with sexuality?
H03: There is no statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort level with sexuality.
Ha3: There is a statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort level with sexuality.
RQ4: What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s willingness to discuss sexual
topics with clients?

86
H04: There is no statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to discuss sexual topics with clients.
Ha4: There is a statistically significant predictive relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to discuss sexual topics with clients.
RQ5: What is the relationship between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of
the sexual comfort of a therapist?
H05: There is no statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of the sexual comfort of a therapist.
Ha5: There is a statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of the sexual comfort of a therapist.
RQ6: What is the relationship between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of a
therapist’s willingness to discuss sexual topics?

87
H06: There is no statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to discuss sexual topics.
Ha6: There is a statistically significant relationship between the independent
variables of a therapist’s age, sex, sexual orientation, number of years in practice, type of
graduate program, relationship status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to discuss sexual topics.
I used eight survey instruments in this study. Cupit (2010) originally used the
demographic questions when studying “counselors, who were members of the American
Counseling Association” (p. 13). The independent variables measured by the
demographic questions were sex, age, strength of religion, sexual orientation, practice
experience, practice setting, and graduate specialization.
I measured sexual knowledge using the 24-Item Miller Fisk Sexual Knowledge
Questionnaire. Harris and Hays (2008) developed the Sexual Comfort Scale using a 7-
point Likert-type scale (1 = uncomfortable; 7 = comfortable) to measure how comfortable
the therapist would be discussing specific sexual topics with clients. Hendrick et al.
(2006) developed the BSAS, which was an update to the authors’ previous scale, the
SAS. The BSAS was appropriate for this study because several researchers used it to
measure the sexual comfort of mental health professionals (see Cupit, 2010; Hanzlik &
Gaubatz, 2012). Harris and Hays (2008) developed the Sexuality Education Scale, which
consists of seven items. Harris and Hays and Cupit (2010) used this scale in their research

88
with marriage and family therapists and counselors incorporating the variables in the
current study. The authors also developed the Experience in Supervision Scale to measure
the number of interactions therapists had while being supervised that involved
discussions of sexuality. Harris and Hays created the Clinical Experience Scale to assess
the aggregate experience therapists had in clinical settings discussing sexual issues. The
final instrument used in the study was the Sexuality Discussion with Clients Scale, which
Harris and Hays developed to assess the willingness of therapists to engage in discussions
with clients about sexual topics.
Chapter 4 is organized by a description of the sample, reliability analysis,
descriptive statistics, data screening, research question and hypothesis testing, and
conclusions. After data collection, I exported the data from Survey Monkey to SPSS 24
for analysis. The following sections provide a description of the data collection process
and participant demographics.
Data Collection
After I obtained the required approval from the Walden IRB and the publishers, I
converted the instruments to an online format for electronic distribution through Survey
Monkey, an online data collection tool. I selected participants from a list of licensed
marriage and family therapists practicing in the United States, who possessed a master’s
or doctoral degree, and who were active in their profession. This list was available for
purchase online. Thereafter, I sent an e-mail explaining the study to 20,000 potential
participants soliciting their participation. I collected data from October 26, 2017 to
November 20, 2017. I had determined that the sample size necessary to meet the effect,

89
power, and alpha for this study was 107 based on a high power of 0.95, a medium effect
size equal to f2 = 0.15, and a significance level of 0.5. I administered 133 surveys, and 90
participants completed them. Thereafter, I performed a post hoc power analysis with a
medium effect size equal to f2 = 0.2, and a significance level of .5 with five predictors and
a sample size of 90, which yielded .90 power. This study had a 90% power to detect
statistically significant associations between the independent and dependent variables
using stepwise linear regression.
I had planned a sampling frame of 2,000 prospective participants, but increased
the sampling frame to 20,000 to achieve the necessary sample size. I had intended to use
chi-square to analyze Hypotheses 5 and 6. However, because the chi-square test returned
too many invalid p values due to over 20% of the cells in the tables being a 0 value, I
substituted the Fisher’s exact test because it also is a test for independence and works
well with smaller sample sizes. This change was successful, and I found statistically
significant results using this method of analysis. There was one change in
instrumentation: I omitted a demographic item about relationship status. This oversight
did not render the results inaccurate but did suggest an item for future research.
Description of Sample
The sample consisted of 90 licensed marriage and family therapists (LMFT). Of
this sample, 81.1% (n = 73) were female and 18.9% (n = 17) were male. I asked the
participants to rate the strength of their religion on a scale of 1 = weak to 5 = strong.
LMFTs had a moderate degree of religious strength (M = 3.37, SD = 1.51) as measured
by Cupit’s (2010) Demographic Data Survey. Participants’ ages ranged from 32 to 78 (M
90
= 56.92, SD = 12.50), and they had been in practice two to 50 years (M = 21.33, SD =
11.70). Regarding practice setting, most participants (70%) were in private practice;
16.7% (n = 15) were in agency settings; and 7.8% (n = 7) were in other settings. Practice
setting data are presented in Table 1.
Table 1
Practice Setting
Setting
n
%
Agency
15
16.7
Hospital
3
3.3
Private practice
63
70.0
School
2
2.2
Other
7
7.8
Total
90
100.0
Regarding graduate specialization, most respondents’ (78.9%, n = 71) graduate
specializations were in marriage, couples, and family. The second most frequent graduate
specialization was clinical mental health and community counseling (8.9%, n = 8). Career
counseling had the least number (2.2%, n = 2) of graduate specializations (see Table 2).
Table 2
Graduate Specialization
Specialization
n
%
Addiction
3
3.3
Career
2
2.2
Clinical mental health/community counseling
8
8.9
Marriage, couple, and family
71
78.9
Other
6
6.7
Total
90
100.0

91
Regarding sexual orientation, most therapists (86.7%, n = 78) were heterosexual;
7.8% (n = 7) were bisexual; 4.4% (n = 4) were homosexual; and 1.1% (n = 1) reported
“other.” The sample was representative of the LMFT profession, as currently 11,350
LMFTs are in private practice (see U.S. Department of Labor, Bureau of Labor Statistics,
2016). Additionally, the sample was reflective because the necessary sample size using
probability sampling techniques was 89, and there were 90 participants.
Instrument Reliability for Sample
I assessed instrument reliability of the sample with Cronbach’s alpha if there was
published reliability for the instrument or variable. In order of variables tested, the results
for sexual knowledge were α = .43; for sexual comfort, the results were α = .86. The
reliability for sexual attitudes indicated that the internal consistency ranged from .71 for
communion to .82 for permissiveness. Willingness to discuss sexual topics had a score of
α = .80, and the score for comfort discussing sexual topics was α = .86. Reliability
coefficients are presented in Table 3.
92
Table 3
Reliability Coefficients for Sample
Variable
N of items
Cronbach’s alpha
Sexual knowledge
24
.431
Sexual attitudes
Permissiveness
10
.825
Communion
5
.712
Instrumentality
5
.747
Willingness to discuss sexual topics
9
.802
Comfort discussing sexual topics
15
.862
Descriptive Statistics
For sexual knowledge on the Miller Fisk Sexual Knowledge Questionnaire, scores
ranged from 6 to 22 (M = 17.36, SD = 2.56). For sexual attitudes (permissiveness), scores
ranged from 1.60 to 5.00 (M = 3.36, SD = 0.78). For sexual attitudes (communion),
scores ranged from 1.00 to 4.20 (M = 2.49, SD = 0.74). For sexual attitudes
(instrumentality), scores ranged from 2.00 to 5.00 (M = 3.61, SD = 0.75). Descriptive
statistics for the variables of interest are presented in Table 4.
93
Table 4
Descriptive Statistics
Variable
Minimum
Maximum
M
SD
Age
32
78
56.92
12.50
Years in practice
2
50
21.33
11.70
Sexual knowledge
6.00
22.00
17.36
2.56
Sexual attitudes (permissiveness)
1.60
5.00
3.36
0.78
Sexual attitudes (communion)
1.00
4.20
2.49
0.74
Sexual attitudes (instrumentality)
2.00
5.00
3.61
0.75
Graduate sexuality training
.00
6.00
2.09
1.25
Supervision experience
.00
4.00
1.13
0.72
Clinical experience
.00
3.00
1.10
0.37
Willingness to discuss sexual topics
1.67
6.33
4.46
1.04
Comfort discussing sexual topics
3.47
6.93
6.02
0.72
I screened the data for normality with skewness and kurtosis statistics. In SPSS,
distributions are considered normal if their absolute values are less than two times their
standard errors. Normal distribution was based on these criteria: age, years in practice,
permissiveness, communion, instrumentality, and willingness to discuss sexual topics.
However, sexual knowledge, graduate sexuality training, supervision experience, clinical
experience, and comfort discussing sexual topics were not normally distributed.
Nevertheless, to preserve the nature of the data, I made no attempt to remediate the
skewed distributions. Skewness and kurtosis coefficients are presented in Table 5.
94
Table 5
Skewness and Kurtosis Coefficients
Variable
Skewness
Kurtosis
Statistic
Std. error
Statistic
Std. error
Age
-.448
.254
-.984
.503
Years in practice
.401
.254
-.727
.503
Sexual knowledge
-1.21
.254
3.57
.503
Sexual attitudes (permissiveness)
-.068
.254
-.669
.503
Sexual attitudes (communion)
.195
.254
-.402
.503
Sexual attitudes (instrumentality)
.205
.254
-.477
.503
Graduate sexuality training
.603
.254
.080
.503
Supervision experience
.892
.254
2.35
.503
Clinical experience
2.59
.254
9.74
.503
Willingness to discuss sexual topics
-.170
.254
-.229
.503
Comfort discussing sexual topics
-1.33
.254
2.10
.503
Research Question 1, Hypothesis 1
What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s willingness to discuss sexual topics
with clients? I investigated Research Question 1, Hypothesis 1 with the Pearson’s r. The
independent variables were attitudes, knowledge, training, supervision experience, and
clinical experience. The dependent variable was a therapist’s willingness to discuss
sexual topics with clients. Table 6 provides the bivariate correlation results.
95
Table 6
Research Question 1 Correlation Results
Variable
Pearson’s r
p
Sexual attitudes (permissiveness)
-.12
.248
Sexual attitudes (communion)
.02
.819
Sexual attitudes (instrumentality)
-.14
.189
Sexual knowledge
-.07
.492
Graduate sexuality training
.31
.003**
Supervision experience
.32
.002**
Clinical experience
.32
.002**
Note. **p < .01; Dependent variable = Willingness to discuss sexual topics. N = 90, two-tailed.
There was no significant relationship between sexual attitudes (permissiveness)
and a therapist’s willingness to discuss sexual topics, r(88) = -.12, p = .248, two-tailed.
There was no significant relationship between sexual attitudes (communion) and a
therapist’s willingness to discuss sexual topics, r(88) = .02, p = .819, two-tailed. There
was no significant relationship between sexual attitudes (instrumentality) and a
therapist’s willingness to discuss sexual topics, r(88) = -.14, p = .189, two-tailed. There
was no significant relationship between sexual knowledge and a therapist’s willingness to
discuss sexual topics, r(88) = -.07, p = .492, two-tailed. There was a significant, positive
relationship between graduate sexuality training and a therapist’s willingness to discuss
sexual topics, r(88) = .31, p = .003, two-tailed. As graduate sexuality training increased,
there was a corresponding increase in a therapist’s willingness to discuss sexual topics.
The coefficient of determination was (r2) = .0961, which means that graduate sexuality
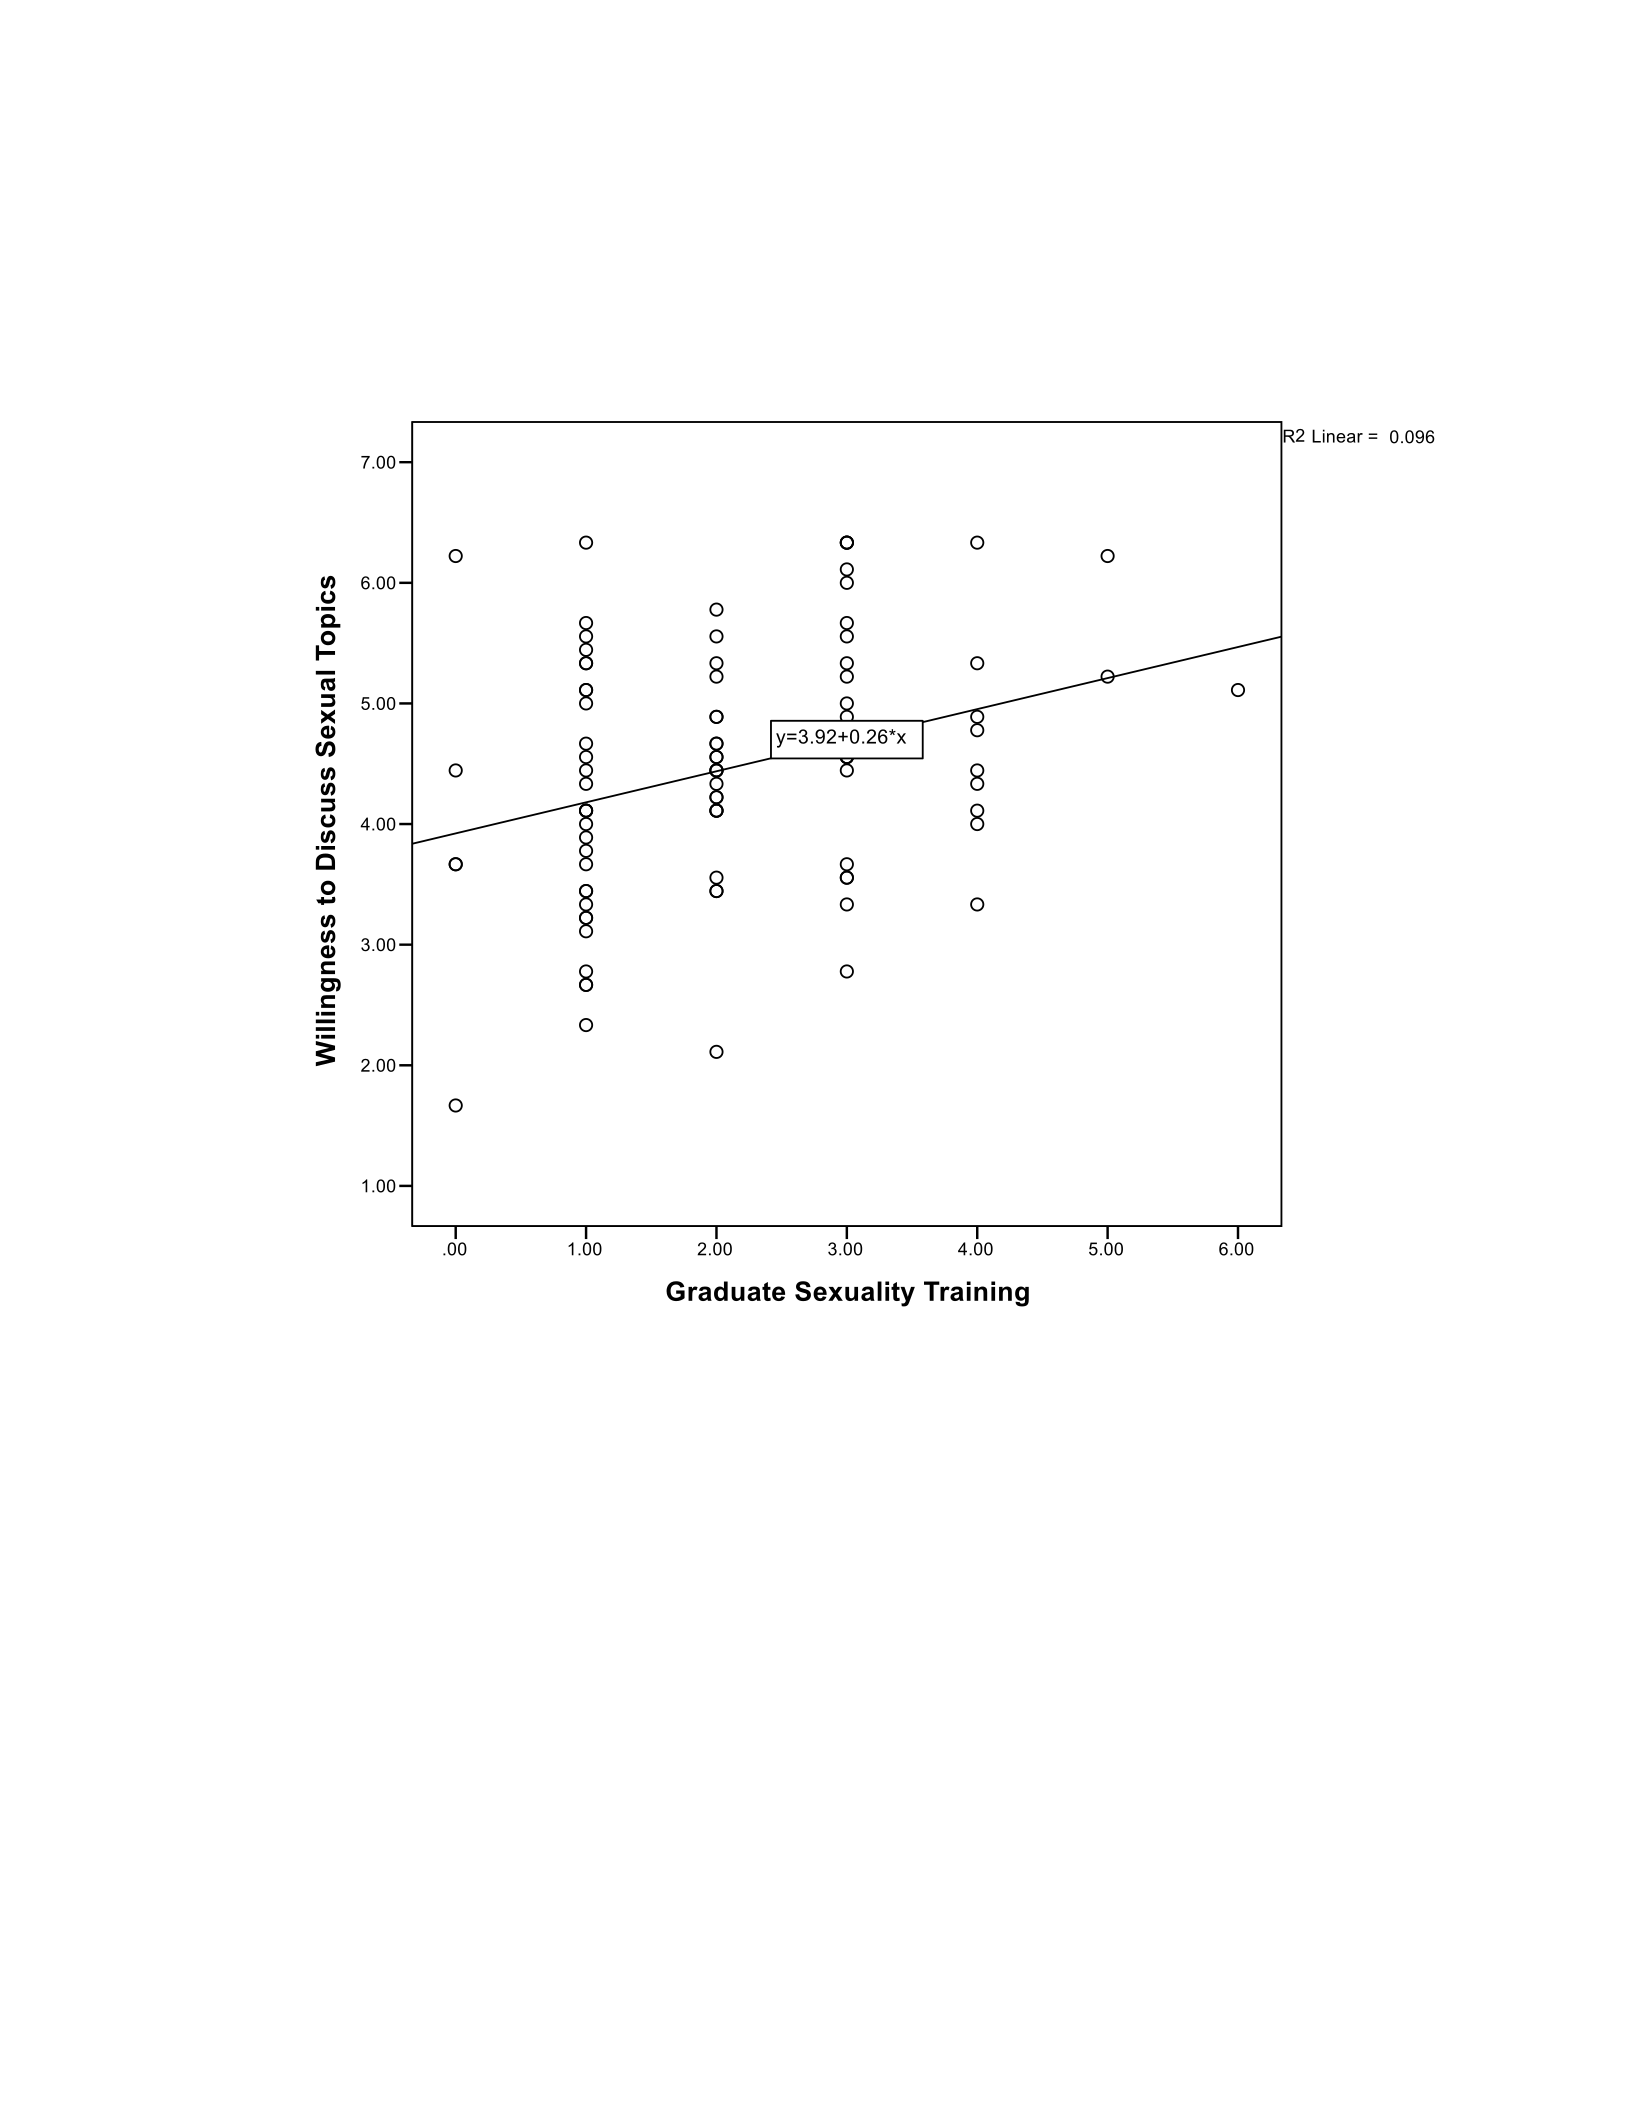
96
training can explain 9.61% of the variance in a therapist’s willingness to discuss sexual
topics. A scatter plot of this relationship is illustrated in Figure 1.
Figure 1. Graduate sexuality training and willingness to discuss sexual topics.
There was a significant, positive relationship between supervision experience and
a therapist’s willingness to discuss sexual topics, r(88) = .32, p = .002, two-tailed. As
supervision experience increased, there was a corresponding increase in a therapist’s
willingness to discuss sexual topics. The coefficient of determination was (r2) = .1024,
which means that the supervision experience can explain 10.24% of the overall variance
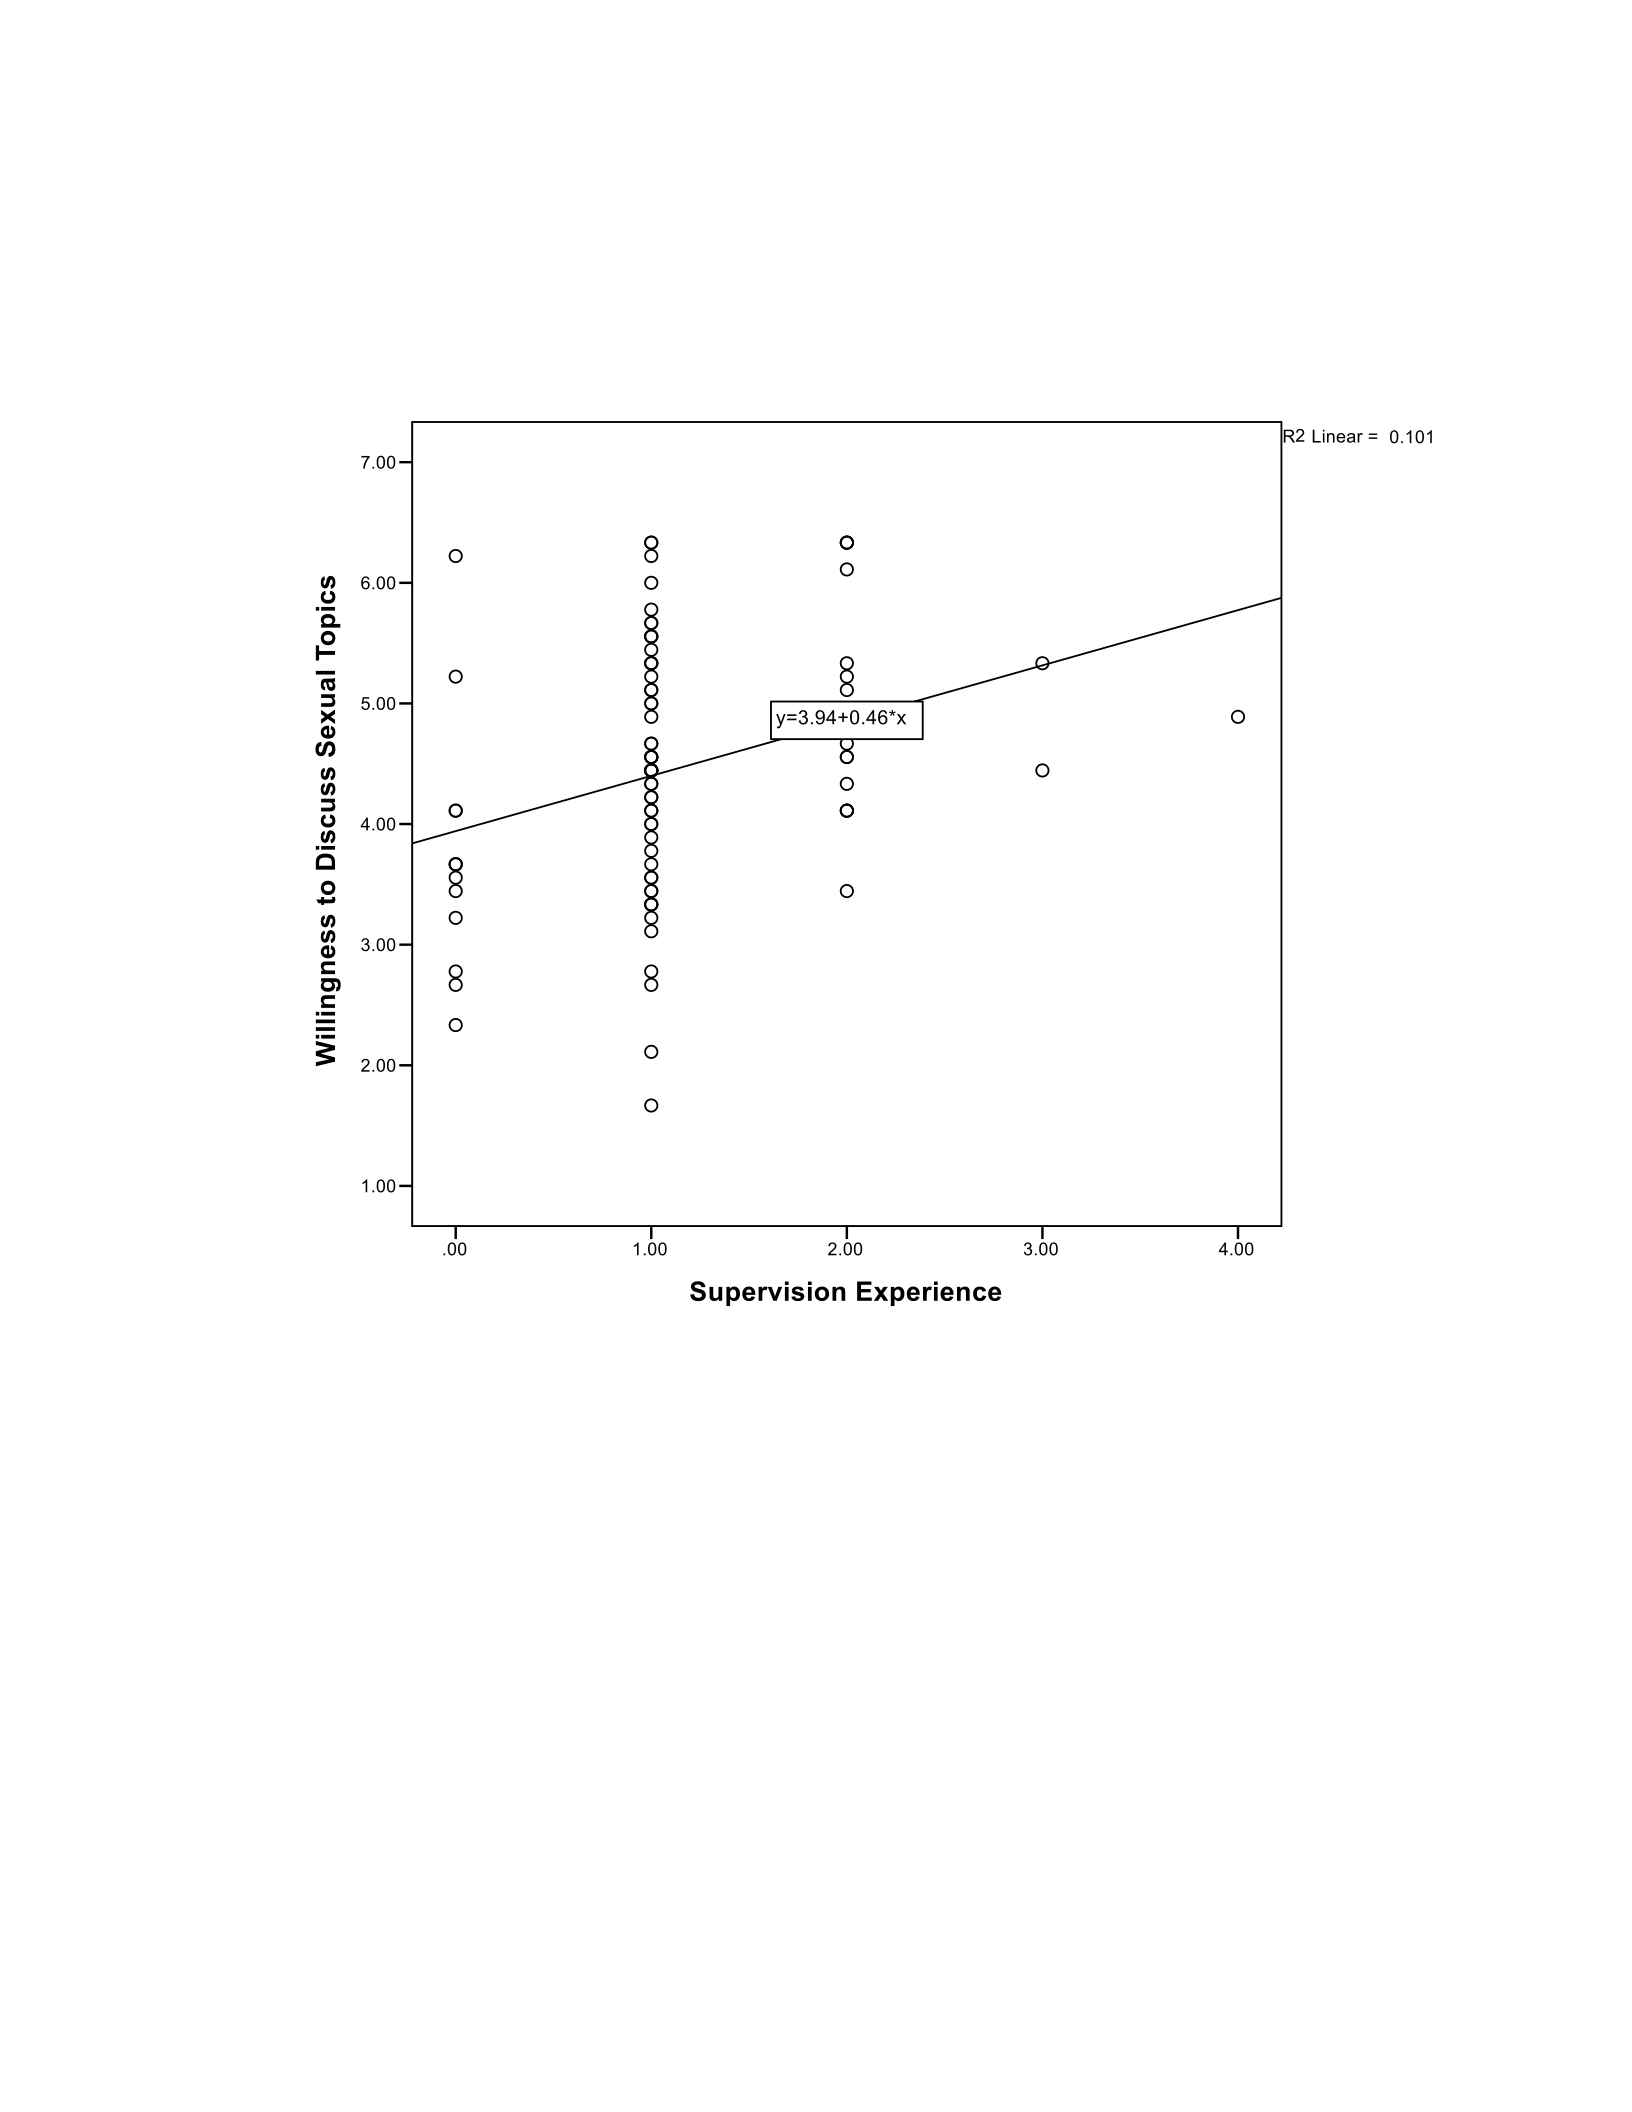
97
in a therapist’s willingness to discuss sexual topics with clients. A scatter plot of this
relationship is illustrated in Figure 2.
Figure 2. Supervision experience and willingness to discuss sexual topics.
There was a significant, positive relationship between clinical experience and a
therapist’s willingness to discuss sexual topics, r(88) = .32, p = .002, two-tailed. As
clinical experience increased, there was a corresponding increase in a therapist’s
willingness to discuss sexual topics. The coefficient of determination was (r2) = .1024,
which means that clinical experience can explain 10.24% of the variance in a therapist’s
willingness to discuss sexual topics.
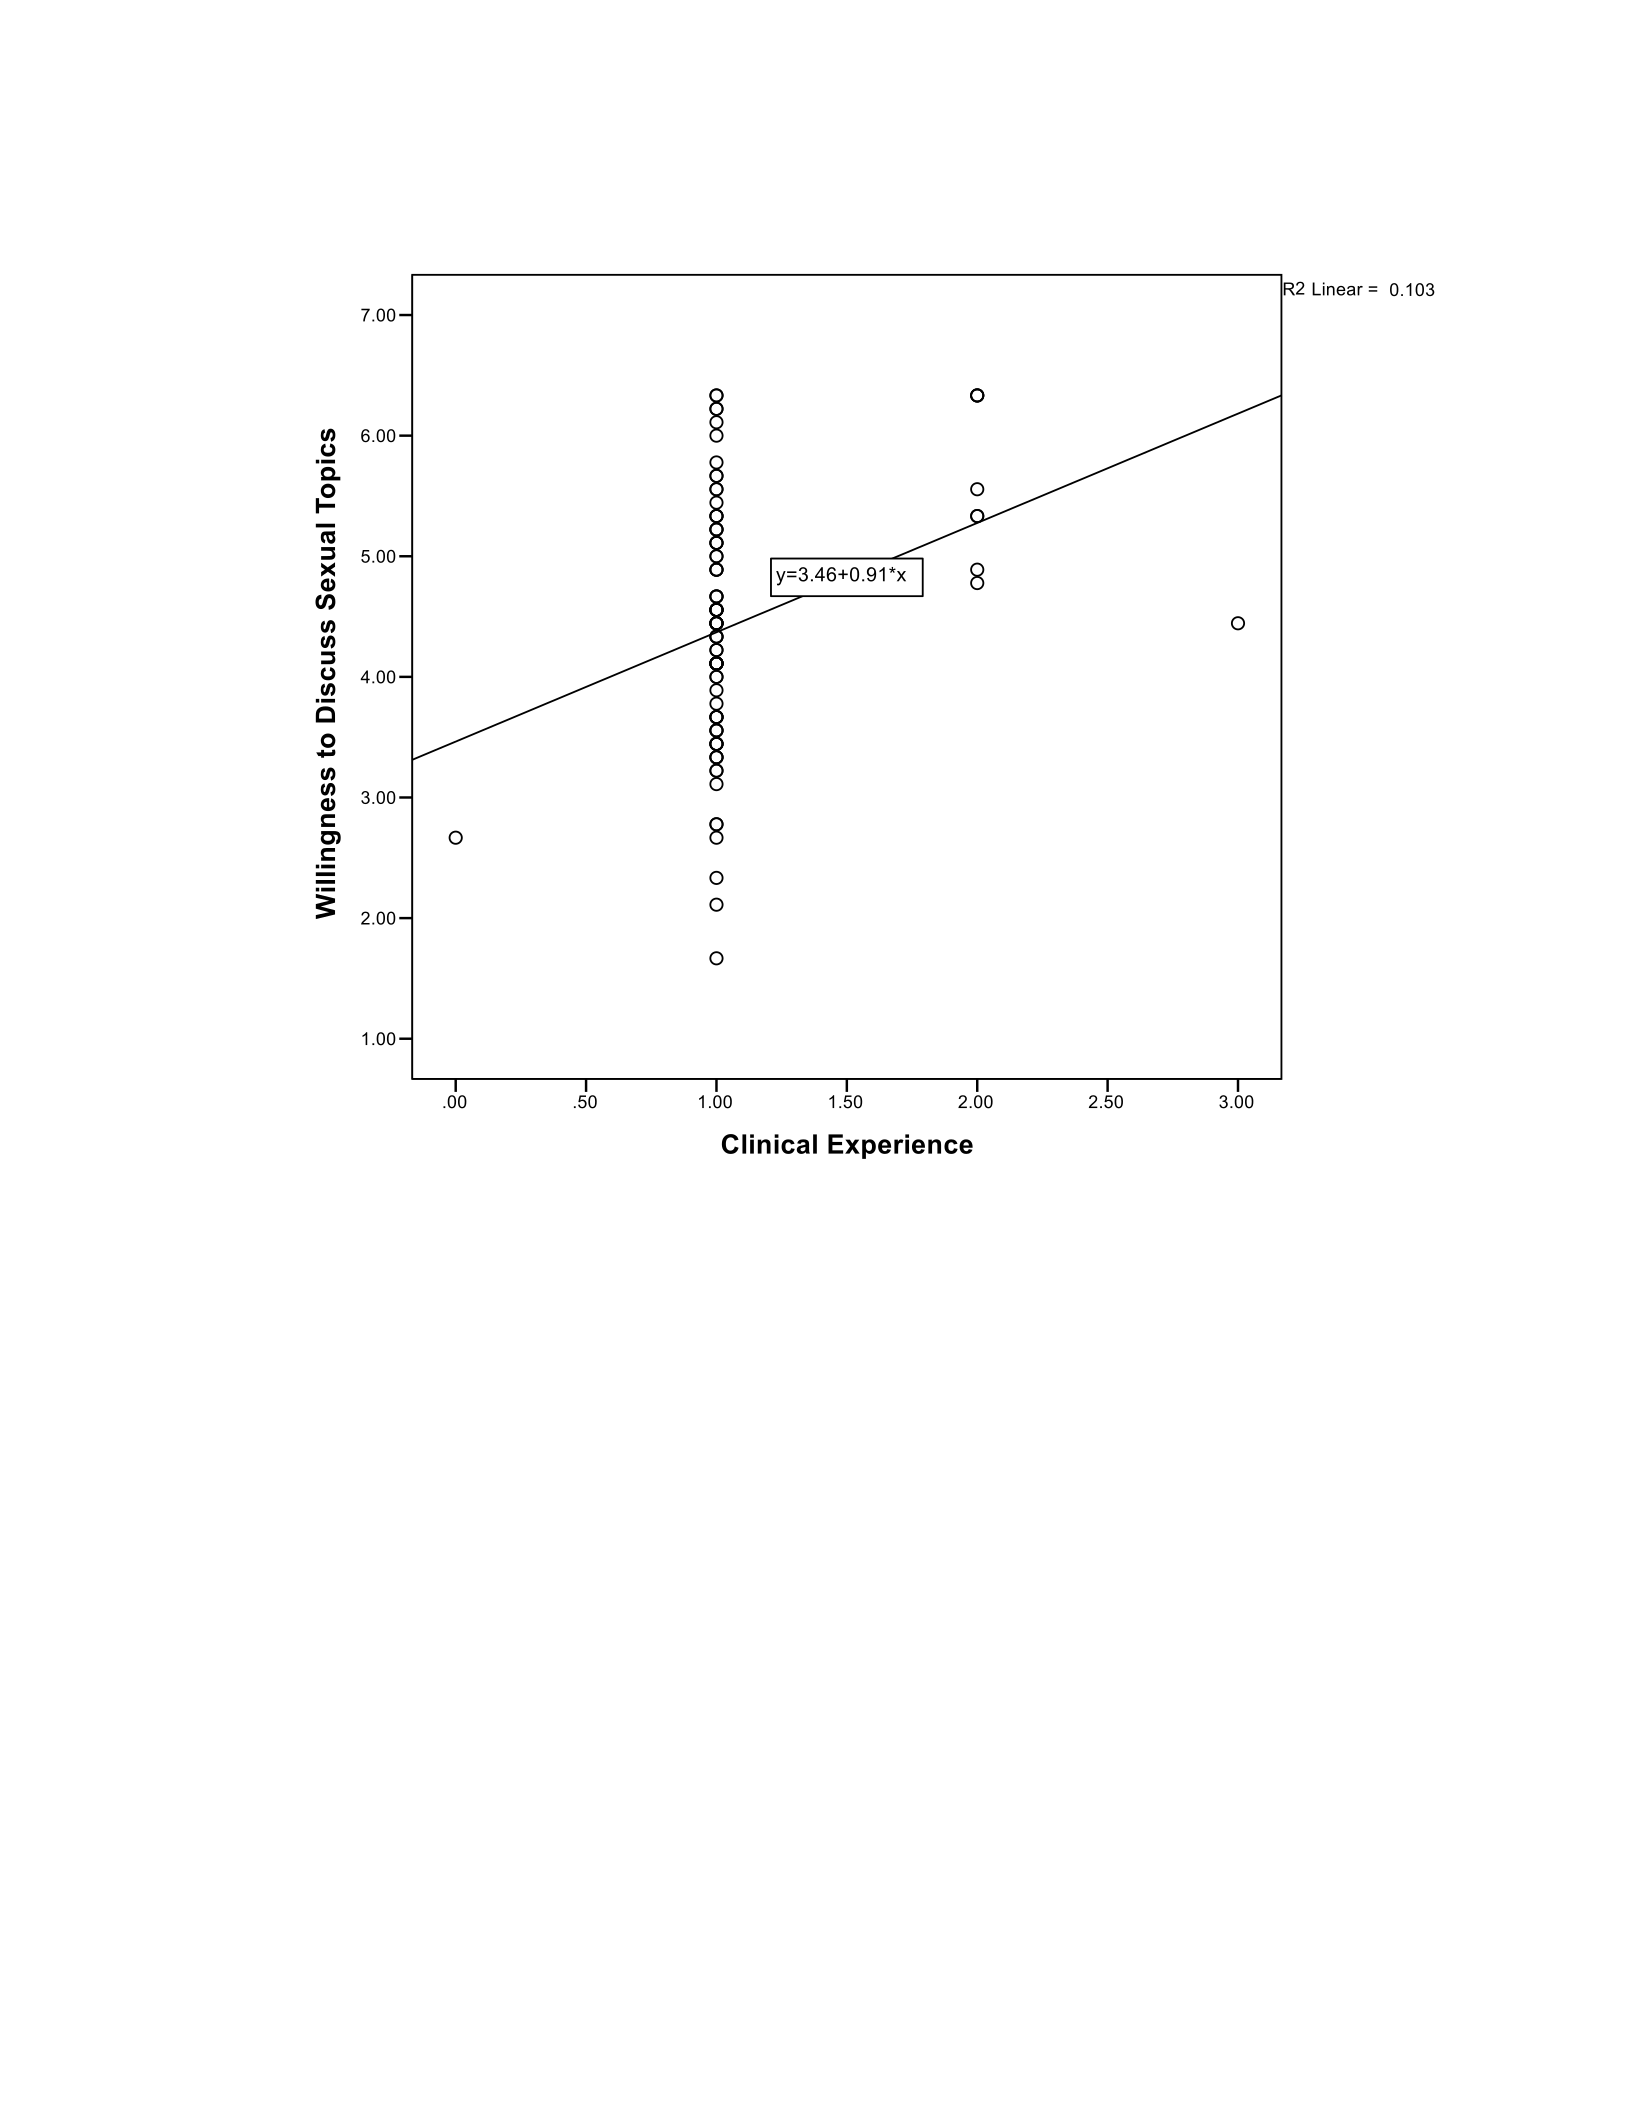
98
Figure 3. Clinical experience and willingness to discuss sexual topics.
H01 stated there is no statistically significant relationship between the independent
variables (attitudes, knowledge, training, supervision experience, and clinical experience)
and the therapists’ willingness to discuss sexual topics with clients. I observed
significance in three out of seven bivariate relationships examined. Therefore, the null
hypothesis was partially rejected.
Research Question 2, Hypothesis 2
What is the relationship between attitudes, knowledge, training, supervision
experience, and clinical experience and a therapist’s comfort discussing sexual topics
99
with clients? I investigated Research Question 2, Hypothesis 2 with the Pearson’s r. The
independent variables were attitudes, knowledge, training, supervision experience, and
clinical experience. The dependent variable was a therapist’s comfort discussing sexual
topics with clients. Table 7 provides the bivariate correlation results.
Table 7
Research Question 2 Correlation Results
Variable
Pearson’s r
p
Sexual attitudes (permissiveness)
-.19
.079
Sexual attitudes (communion)
.04
.731
Sexual attitudes (instrumentality)
.10
.374
Sexual knowledge
.08
.462
Graduate sexuality training
.19
.078
Supervision experience
.11
.324
Clinical experience
.01
.931
Note. Dependent variable = Comfort discussing sexual topics. N = 90, two-tailed.
There was no significant relationship between sexual attitudes (permissiveness)
and a therapist’s comfort discussing sexual topics, r(88) = -.19, p = .079, two-tailed.
There was no significant relationship between sexual attitudes (communion) and a
therapist’s comfort discussing sexual topics, r(88) = .04, p = .731, two-tailed. There was
no significant relationship between sexual attitudes (instrumentality) and a therapist’s
comfort discussing sexual topics, r(88) = .10, p = .374, two-tailed. There was no
significant relationship between sexual knowledge and a therapist’s comfort discussing
sexual topics, r(88) = .08, p = .462, two-tailed. There was no significant relationship
between graduate sexuality training and a therapist’s comfort discussing sexual topics,

100
r(88) = .19, p = .078, two-tailed. There was no significant relationship between
supervision experience and a therapist’s comfort discussing sexual topics, r(88) = .11, p
= .324, two-tailed. There was no significant relationship between clinical experience and
a therapist’s comfort discussing sexual topics, r(88) = .01, p = .931, two-tailed.
H02 stated that there is no statistically significant relationship between the
independent variables (attitudes, knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort discussing sexual topics with clients. I
observed no significant relationships between the independent variables (attitudes,
knowledge, training, supervision experience, and clinical experience) and the therapists’
comfort discussing sexual topics with clients. Significance values ranged from p = .078 to
p = .931. Therefore, the null hypothesis was accepted.
Research Question 3, Hypothesis 3
What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s comfort level with sexuality? I
tested Research Question 3, Hypothesis 3 with stepwise multiple linear regression. The
independent variables were attitudes, knowledge, training, supervision experience, and
clinical experience. The dependent variable was a therapist’s comfort level with sexuality.
I entered no variables into the equation as determined by SPSS. When using stepwise
multiple linear regression, if none of the independent variables are significantly related to
the outcome variable, no model is generated.
H03 stated that there is no statistically significant predictive relationship between
the independent variables (attitudes, knowledge, training, supervision experience, and

101
clinical experience) and a therapist’s comfort level with sexuality. Since this SPSS
analysis generated no regression model, there was no statistically significant predictive
relationship between the independent variables (attitudes, knowledge, training,
supervision experience, and clinical experience) and a therapist’s comfort level with
sexuality. Therefore, the null hypothesis was accepted.
Research Question 4, Hypothesis 4
What independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) predict a therapist’s willingness to discuss sexual
topics with clients? I investigated Research Question 4, Hypothesis 4 with stepwise
multiple linear regression. The independent variables were sexual attitudes, knowledge,
training, supervision experience, and clinical experience. The dependent variable was the
therapists’ willingness to discuss sexual topics with clients.
During the analysis, I also examined the residuals. A residual is the difference
between the observed and the predicted values of the dependent variable. Standardized
residuals greater than ±3 are candidates for exclusion. Standardized residuals ranged from
-2.79 to 2.39 and were, therefore, within normal limits. A normal P-P Plot was also
generated to illustrate that the residuals were normally distributed. A normal distribution
is evidenced by the proximity of the plotted values for the residuals along the 45-degree
line in Figure 4.
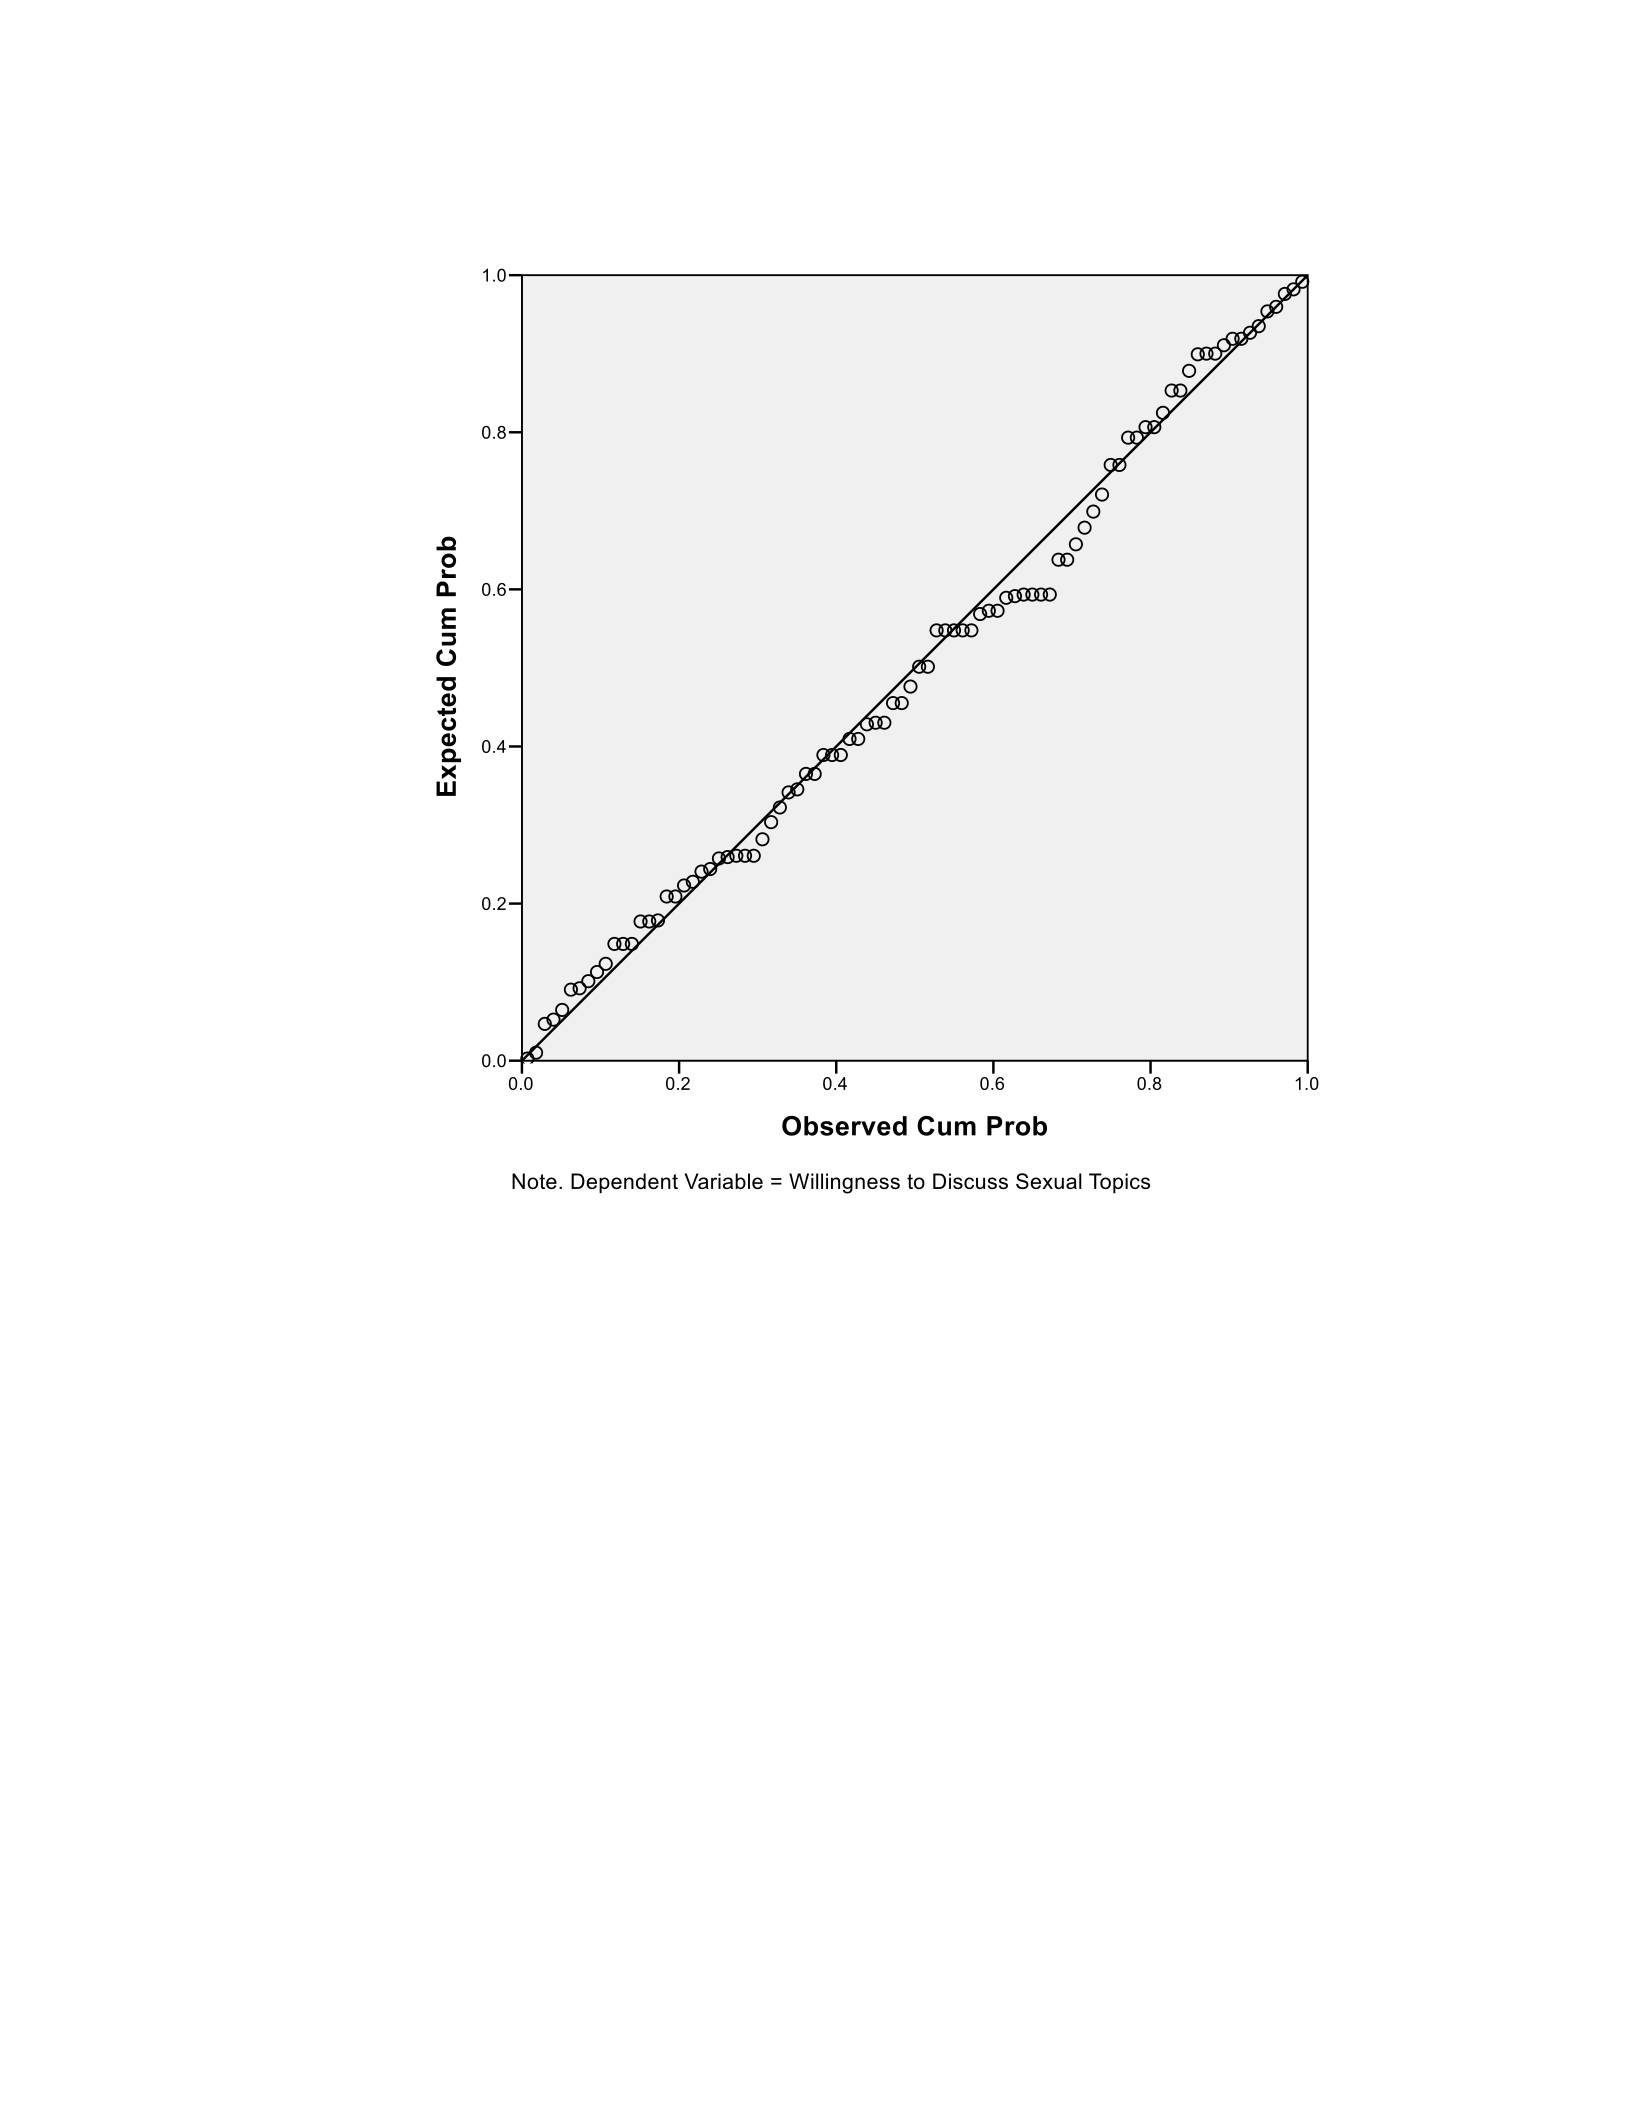
102
Figure 4. Normal P-P plot for regression standardized residuals.
The independence of the error terms was examined with a scatter plot of the
regression standardized residuals by the standardized predicted values. Independence of
the error terms is illustrated by a relatively random pattern of points along the horizontal
line (See Figure 5).
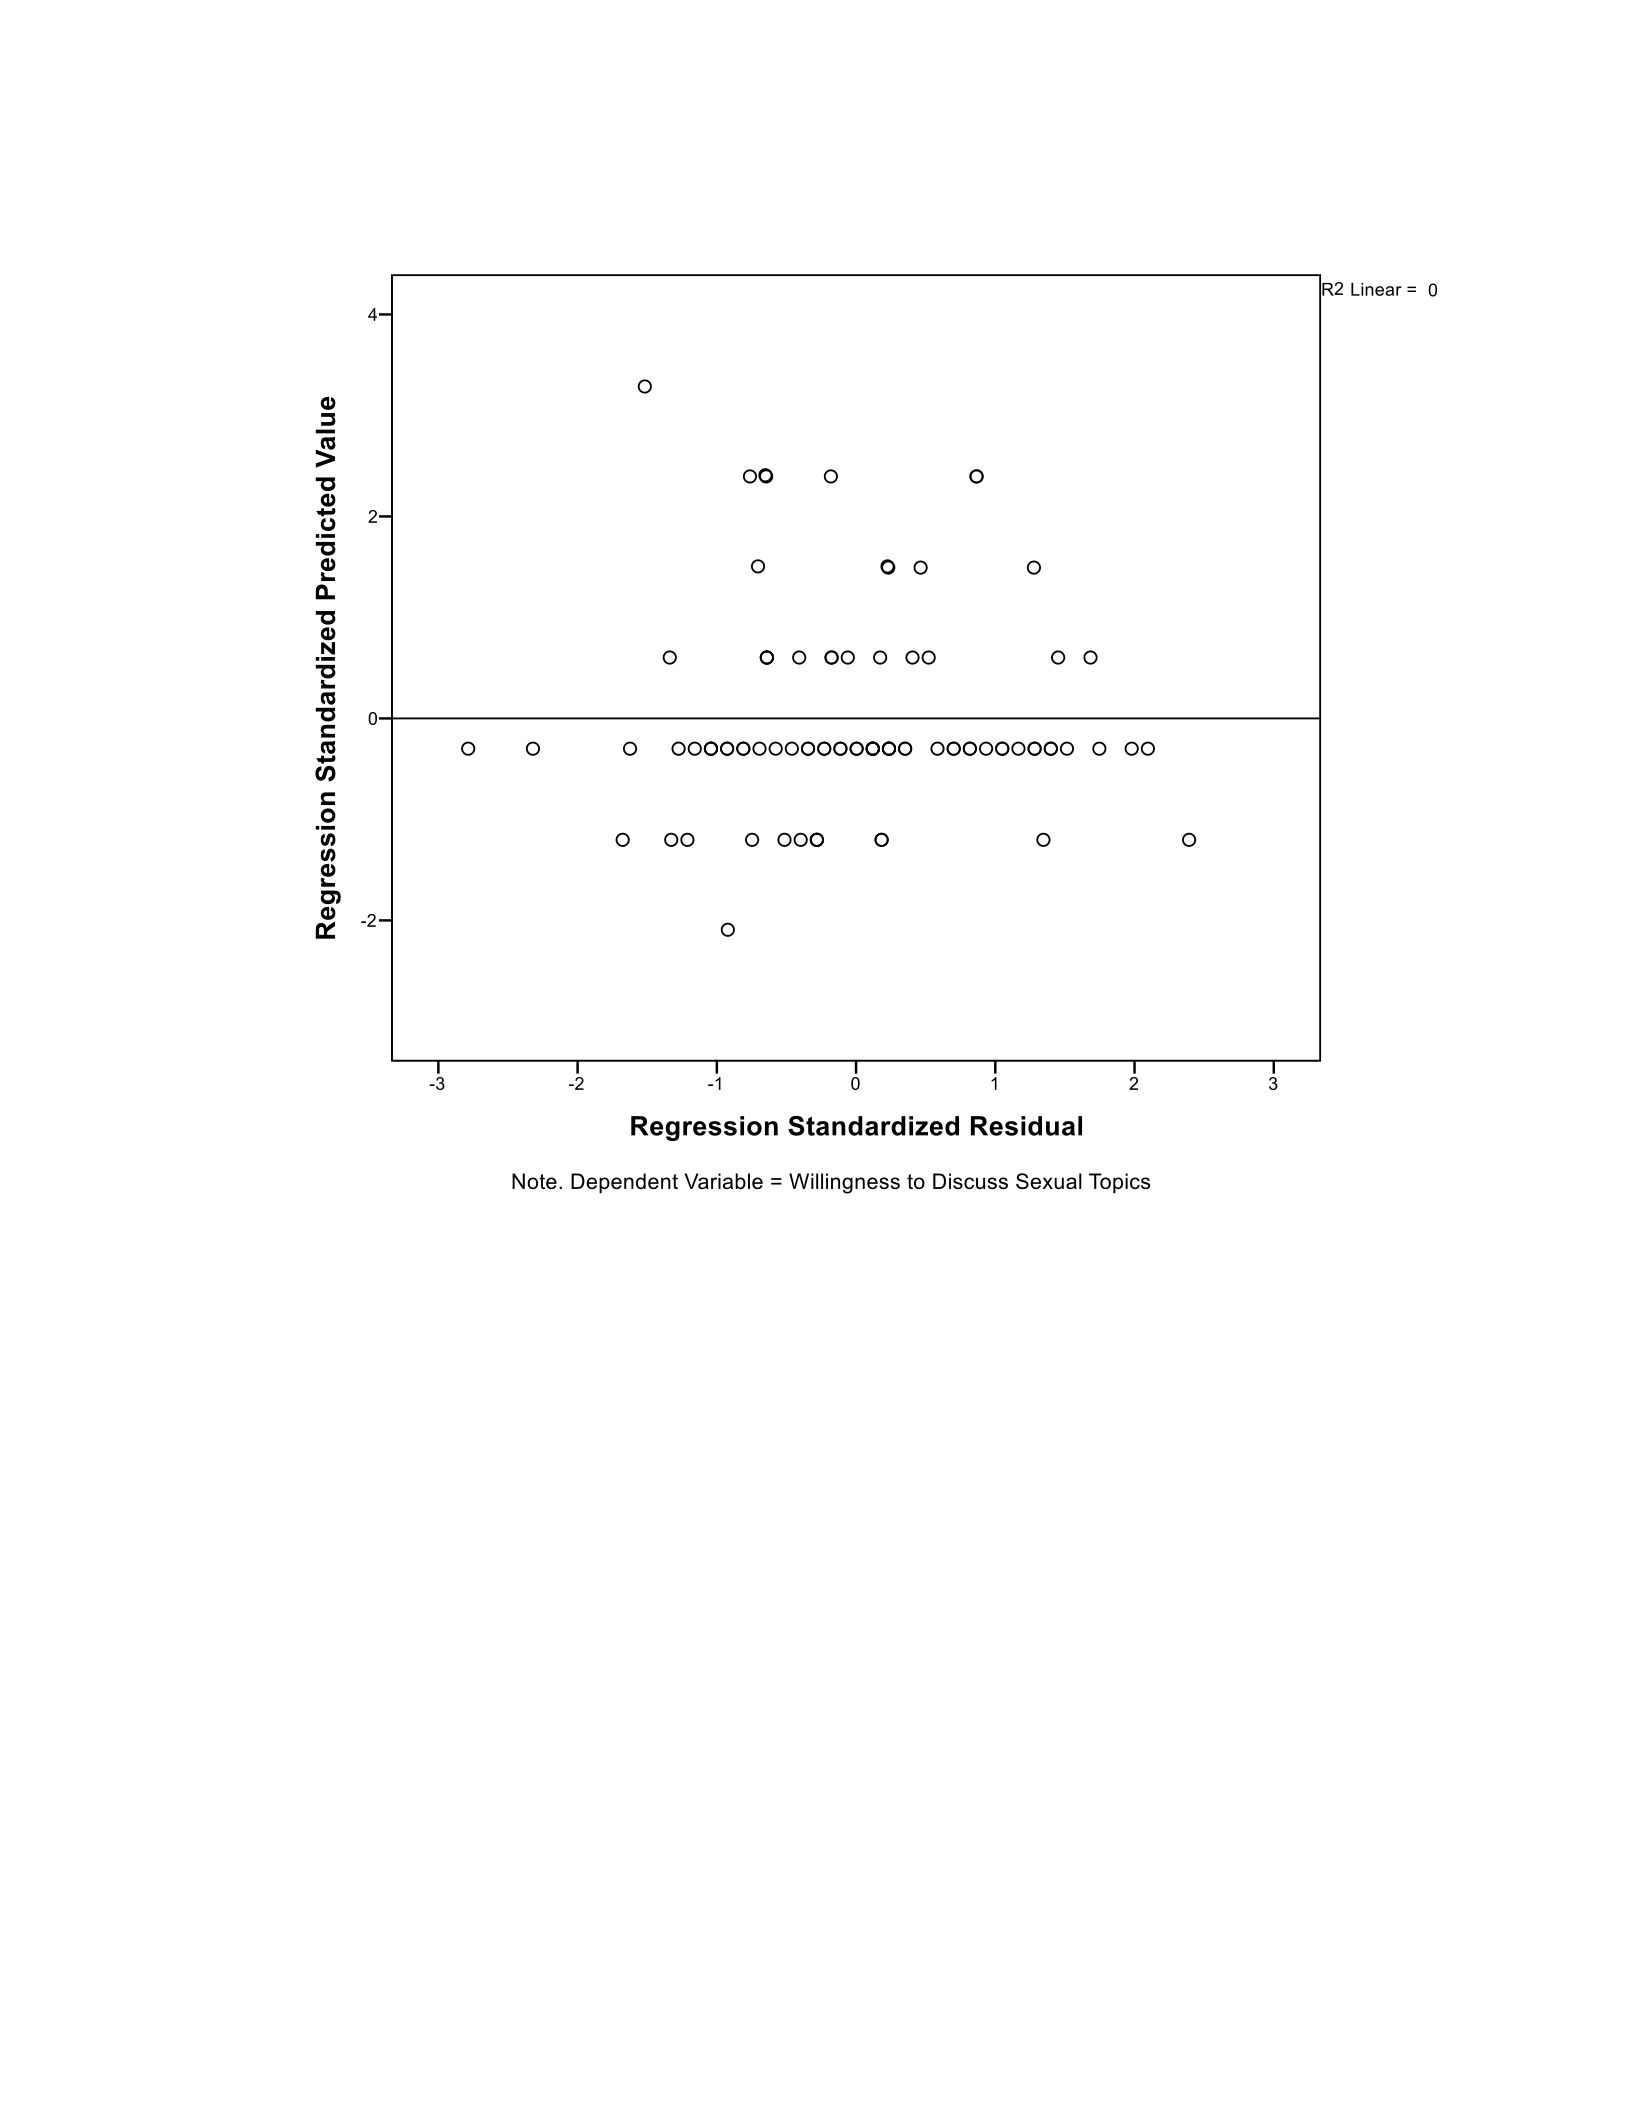
103
Figure 5. Scatterplot of standardized residuals by standardized predicted values.
A regression model was generated from the stepwise procedure, F(2, 87) = 9.28, p
< .001; R2 = .18. Examination of the univariate statistics included in the model revealed
that clinical experience (β = 0.27, t = 2.81, p = .006) and supervision experience (β =
0.27, t = 2.77, p = .007) were the two variables that predicted willingness to discuss
sexual topics. Regression coefficients are presented in Table 8.
104
Table 8
Regression Coefficients
Variable
B
SE B
β
t
p
Step 1
(Constant)
3.46
0.33
10.48
.000
Clinical experience**
0.91
0.29
0.32
3.18
.002
Step 2
(Constant)
3.15
0.34
9.34
.000
Clinical experience**
0.78
0.28
0.28
2.81
.006
Supervision experience**
0.39
0.14
0.27
2.77
.007
Note. Dependent variable: Willingness to discuss sexual topics. R2 = .32 for Step 1. R2
= .18 for Step 2; **p < .01; N = 90.
H04 stated that there was no statistically significant predictive relationship
between the independent variables (attitudes, knowledge, training, supervision
experience, and clinical experience) and a therapist’s willingness to discuss sexual topics
with clients. Examination of the univariate statistics included in the model revealed that
clinical experience (β = 0.28, t = 2.81, p = .006) and supervision experience (β = 0.27, t =
2.77, p = .007) were the two variables that predicted willingness to discuss sexual topics.
Therefore, the null hypothesis was partially rejected.
Research Question 5, Hypothesis 5
What is the relationship between the independent variables of a therapist’s age,
sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of
the sexual comfort of a therapist? Research Question 5, Hypothesis 5 was investigated
with the Pearson’s r. The independent variables were a therapist’s age, sex, sexual
orientation, number of years in practice, type of graduate program, relationship status,
practice setting, and strength of religion. The dependent variable was a therapist’s

105
comfort discussing sexual topics with clients. Table 9 provides the bivariate correlation
results.
Table 9
Research Question 5 Correlation Results
Variable
Pearson’s r
p
Age
.04
.701
Sex
-.03
.770
Sexual orientation
-.02
.834
Years in practice
.09
.385
Graduate specialization
.05
.676
Practice setting
-.12
.265
Strength of religion
.01
.894
Note. Dependent Variable = Comfort discussing sexual topics. N = 90, two-tailed; Sex: 1=Female, 0=Male,
Sexual Orientation: 1=Heterosexual, 0=Other, Graduate specialization: 1=Marriage and family, 0=Other,
Practice setting: 1=Private practice, 0=Other, strength of religion: 1=Strong, 0=Other.
There was no significant relationship between the age of the therapist and a
therapist’s comfort discussing sexual topics, r(88) = .04, p = .701, two-tailed. There was
no significant relationship between the sex of a therapist and a therapist’s comfort
discussing sexual topics, r(88) = -.03, p = .770, two-tailed. There was no significant
relationship between a therapist’s sexual orientation and a therapist’s comfort discussing
sexual topics, r(88) = -.02, p = .834, two-tailed. There was no significant relationship
between a therapist’s years in practice and a therapist’s comfort discussing sexual topics,
r(88) = .09, p = .385, two-tailed. There was no significant relationship between a
therapist’s graduate specialization and a therapist’s comfort discussing sexual topics,
r(88) = .05, p = .676, two-tailed. There was no significant relationship between a

106
therapist’s practice setting and a therapist’s comfort discussing sexual topics, r(88) =
-.12, p = .265, two-tailed. There was no significant relationship between a therapist’s
strength of religion and a therapist’s comfort discussing sexual topics, r(88) = .01, p
= .894, two-tailed.
Table 10 presents the p values for the Fisher’s exact tests between the willingness
to discuss questions, as measured by the Sexuality Discussions with Clients Scale, and
the independent variables, which are gender, strength of religion, age, years of practice,
practice setting, graduate program, and sexual orientation. A statistically significant
association, and thus the rejection of statistical independence of distributions, is defined
in this analysis as p ≤ 0.05.
Table 10
Sexual Discussions With Clients Scale Fisher’s Exact Test Results
SDCS*
Gender
Strength
of
religion
Age
Years of
practice
Practice
setting
Graduate
program
Sexual
orientation
1
.219
.099
.253
.301
.995
.244
.648
2
.867
.625
.774
.599
.261
.398
.188
3
.145
.5
.732
.629
.126
.654
.611
4
.791
.577
.606
.743
.159
.342
.722
5
.779
.78
.165
.665
.919
.16
.356
6
.153
.595
.9
.411
.628
.984
.413
7
.142
.525
.644
.09
.386
.969
.591
8
.05
.904
.968
.244
.288
.597
.245
9
.679
.654
.484
.764
.751
.083
.835
*Sexuality Discussions with Clients Scale
For Question 1 of the scale, willingness to discuss STDs/STIs, none of the
independent variables demonstrated statistically significant p values. For gender, it was

107
0.219; for strength of religion, 0.099; for age, 0.253; for years of practice, 0.301; for
practice setting, 0.995, for graduate program, 0.244; and for sexual orientation, 0.648.
The results of these tests suggest that demographic characteristics do not influence the
therapists’ willingness to discuss sexually transmitted diseases or infections. Similarly,
there was not a statistically significant dependency for Question 2, willingness to discuss
sexual dysfunction, on the independent demographic variables. The p value for gender
was 0.867; for strength of religion, 0.625; for age, 0.774; for years of practice, 0.599; for
practice setting, 0.261, for graduate program, 0.398; and for sexual orientation, 0.188.
The results of these tests imply that demographic traits do not associate with the
therapists’ willingness to discuss sexual dysfunction issues.
For Question 3, willingness to discuss client satisfaction with their sexual life, the
p value with gender was 0.145; with strength of religion, 0.5; with age, 0.732; with years
of practice, 0.629; with practice setting, 0.126, with a graduate program, 0.654; and with
sexual orientation, 0.611. As such, a therapist’s willingness to discuss a client’s sexual
satisfaction does not a have statistically significant dependency on demographic traits.
Concerning Question 4, willingness to discuss clients’ typical sexual interaction pattern,
the p value with gender was 0.791; with strength of religion, 0.577; with age, 0.606; with
years of practice, 0.743; with practice setting, 0.159, with a graduate program, 0.342; and
with sexual orientation, 0.722. Thus, demographic characteristics do not possess an
apparent association with a therapist’s willingness to discuss the client’s typical sexual
interaction pattern.

108
For Question 5, willingness to discuss reproduction and contraception, the p value
with gender was 0.779; with strength of religion, 0.78; with age, 0.165; with years of
practice, 0.665; with practice setting, 0.919, with a graduate program, 0.16; and with
sexual orientation, 0.356. Therefore, willingness to discuss reproduction or contraception
do not exhibit a clear relationship with any of the demographic traits. Concerning
Question 6, willingness to discuss sexual orientation, the p value with gender was 0.153;
with strength of religion, 0.595; with age, 0.9; with years of practice, 0.411; with practice
setting, 0.628, with a graduate program, 0.984; and with sexual orientation, 0.413. In
effect, the willingness to discuss sexual orientation does not appear to be contingent on
any demographic attribute.
For Question 7, willingness to discuss sexual relationship enhancement, the p
value with gender was 0.142; with strength of religion, 0.525; with age, 0.644; with years
of practice, 0.09; with practice setting, 0.386, with a graduate program, 0.969; and with
sexual orientation, 0.591. Because of these statistically insignificant values,
demographics may not influence the willingness to discuss sexual relationship
enhancement.
Concerning Question 8, willingness to discuss sexual abuse, gender was
statistically significant (p = 0.05), which indicates that the therapists’ gender may
associate how willing they are to discuss sexual abuse. For the other independent
variables, however, no statistically significant relationship was found and thus may not
associate with this dependent variable. The p value with strength of religion was 0.904;
with age, 0.968; with years of practice, 0.244; with practice setting, 0.288, with a

109
graduate program, 0.597; and with sexual orientation, 0.245. For Question 9, willingness
to discuss sexually related issues when the client states that it is a concern, the p value
with gender was 0.679; with strength of religion, 0.654; with age, 0.484; with years of
practice, 0.764; with practice setting, 0.751, with a graduate program, 0.083; and with
sexual orientation, 0.835. Because these p values exceeded the threshold of 0.05, I
accepted the null hypothesis that the distribution of the dependent variable and the
demographic variables were independent of each other.
As a whole, willingness to discuss sexually related topics, as defined within the
constructs of the Sexuality Discussion with Clients Scale, may not be dependent on the
therapists’ demographic characteristics except gender, which may influence how willing
they are to discuss sexual abuse with their clients.
H05 stated that there is no statistically significant relationship between the
independent variables of a therapist’s age, sex, sexual orientation, number of years in
practice, type of graduate program, relationship status, practice setting, or strength of
religion and the dependent variable of the sexual comfort of a therapist. I observed no
significant relationships in the Pearson’s r. Therefore, the null hypothesis was accepted as
to the Pearson’s r results. However, there was one statistically significant relationship
found by Fisher’s exact test, gender: gender, p = .05, was statistically significant when it
came to a willingness to discuss sexual abuse. Therefore, the null hypothesis was
partially rejected.

110
Research Question 6, Hypothesis 6
What is the relationship between the independent variables of a therapist’s age,
sex, sexual orientation, number of years in practice, type of graduate program,
relationship status, practice setting, or strength of religion and the dependent variable of a
therapist’s willingness to discuss sexual topics? I investigated Research Question 6,
Hypothesis 6 with the Pearson’s r. The independent variables were a therapist’s age, sex,
sexual orientation, number of years in practice, type of graduate program, relationship
status, practice setting, and strength of religion. The dependent variable was a therapist’s
comfort discussing sexual topics with clients. Table 10 provides the bivariate correlation
results.
Table 11
Research Question 6 Correlation Results
Variable
Pearson’s r
p
Age
.06
.552
Sex
-.02
.874
Sexual orientation
-.004
.967
Years in practice
.12
.260
Graduate specialization
-.20
.063
Practice setting
.22
.036*
Strength of religion
.06
.588
Note. *p < .05; Dependent Variable = Willingness to discuss sexual topics. N = 90, two-tailed; Sex:
1=Female, 0=Male, Sexual orientation: 1=Heterosexual, 0=Other, graduate specialization: 1=Marriage and
family, 0=Other, Practice setting: 1=Private practice, 0=Other, strength of religion: 1=Strong, 0=Other.
There was no significant relationship between the age of the therapist and the
therapists’ willingness to discuss sexual topics, r(88) = .06, p = .552, two-tailed. There

111
was no significant relationship between the sex of a therapist and a therapist’s willingness
to discuss sexual topics, r(88) = -.02, p = .874, two-tailed. There was no significant
relationship between a therapist’s sexual orientation and a therapist’s willingness to
discuss sexual topics, r(88) = -.004, p = .967, two-tailed. There was no significant
relationship between a therapist’s years in practice and a therapist’s willingness to discuss
sexual topics, r(88) = .12, p = .260, two-tailed. There was no significant relationship
between a therapist’s graduate specialization and a therapist’s willingness to discuss
sexual topics, r(88) = -.20, p = .063, two-tailed. There was a significant relationship
between a therapist’s practice setting and a therapist’s willingness to discuss sexual
topics, r(88) = .22, p = .036, two-tailed. The coding of the variable for practice setting
means that therapists who are willing to discuss sexual topics are more likely to be in
private practice than in other settings. The coefficient of determination was (r2) = .0484,
which means that the practice setting can explain 4.84% of the variance in a therapist’s
willingness to discuss sexual topics. There was no significant relationship between a
therapist’s strength of religion and a therapist’s willingness to discuss sexual topics, r(88)
= .06, p = .588, two-tailed.
Table 12 displays the p values for the Fisher’s exact tests between the variable of
comfort while discussing sexuality questions and the independent variables, which are
gender, strength of religion, age, years of practice, practice setting, graduate program, and
sexual orientation. A statistically significant association, and thus, the rejection of
statistical independence of distributions, is defined in this analysis as p < 0.05.

112
For Question 1, comfortable to discuss with clients, none of the independent
variables demonstrated statistically significant p values. For gender, it was 0.877; for
strength of religion, 0.633; for age, 0.173; for years of practice, 0.36; for practice setting,
0.596, for graduate program, 0.26; and for sexual orientation, 0.704. The results of these
tests suggest that demographic characteristics do not influence a therapist’s
comfortability to discuss sexually-related topics with clients. Similarly, there was not a
statistically significant dependency for Question 2, comfortable to discuss with students
and trainees, on the independent demographic variables. The p value for gender was
0.871; for strength of religion, 0.101; for age, 0.183; for years of practice, 0.564; for
practice setting, 0.71, for graduate program, 0.309; and for sexual orientation, 0.522. The
results of these tests imply that demographic traits do not associate with a therapist’s
comfort to discuss sexually-related topics with students and trainees.
For Question 3, comfortable to discuss with supervisors, the p value with gender
was 0.587; with strength of religion, 0.454; with age, 0.064; with years of practice, 0.862;
with practice setting, 0.083, with a graduate program, 0.535; and with sexual orientation,
0.399. As such, a therapist’s comfortability to discuss with supervisors does not have a
statistically significant dependency on demographic traits. Concerning Question 4,
comfortable to discuss with colleagues, the p value with gender was 0.811; with strength
of religion, 0.051; with age, 0.394; with years of practice, 0.864; with practice setting,
0.608, with a graduate program, 0.055; and with sexual orientation, 0.689. Thus,
demographic characteristics do not possess an apparent association with a therapist’s
comfortability to discuss with colleagues.

113
For Question 5, respond openly and confidently when sexual values are
challenged, the p value with gender was 0.532; with strength of religion, 0.452; with age,
0.717; with years of practice, 0.392; with practice setting, 0.912, with a graduate
program, 0.093; and with sexual orientation, 0.265. Therefore, demographic traits do not
appear to influence a therapist’s behavior when their sexual values are challenged.
Concerning Question 6, communicate effectively about sexuality, the p value with gender
was 0.524; with strength of religion, 0.598; with age, 0.022; with years of practice, 0.02;
with practice setting, 0.827, with a graduate program, 0.869; and with sexual orientation,
0.444. In effect, the age of the therapist and years of practice may influence effective
communication regarding sexually-related topics; for the other independent variables,
such an association does not exist in these results.
For Question 7, use of appropriate sexual vocabulary, the p value with gender was
0.443; with strength of religion, 0.48; with age, 0.27; with years of practice, 0.173; with
practice setting, 0.96, with a graduate program, 0.665; and with sexual orientation, 0.417.
Because of these statistically insignificant values, demographics may not influence a
therapist’s use of appropriate sexual vocabulary. Concerning Question 8, sensitive and
respectful of feelings and anxieties toward sexual matters, the p value with gender was
0.438; with strength of religion, 0.842; with age, 0.084; with years of practice, 0.498;
with practice setting, 0.911, with a graduate program, 0.663; and with sexual orientation,
0.247. Because of these statistically insignificant values, demographics may not affect a
therapist’s sensitivity and respectfulness toward their clients’ sexual matters.

114
For Question 9, encourage clients to explore their sexual values, the p value with
gender was 0.711; with strength of religion, 0.795; with age, 0.742; with years of
practice, 0.243; with practice setting, 0.843, with a graduate program, 0.198; and with
sexual orientation, 0.671. The statistically insignificant results indicate that encouraging
clients to explore their sexual values is not associated with demographic traits.
For Question 10, unconcerned about influencing client’s sexuality, the p value
with gender was 0.662; with strength of religion, 0.797; with age, 0.966; with years of
practice, 0.012; with practice setting, 0.549, with a graduate program, 0.28; and with
sexual orientation, 0.786. The statistically significant value with the years of experience a
therapist has in their practice suggests that they may influence how concerned a therapist
is about influencing a client’s sexuality. For the other independent variables, such an
association does not appear to exist in these results.
For Question 11, confidence in sexuality knowledge, the p value with gender was
0.787; with strength of religion, 0.261; with age, 0.572; with years of practice, 0.554;
with practice setting, 0.303, with a graduate program, 0.355; and with sexual orientation,
0.606. The statistically insignificant results indicate that confidence in sexuality
knowledge is not contingent on demographic traits. Concerning Question 12, appearing
poised, the p value with gender was 0.977; with strength of religion, 0.921; with age,
0.68; with years of practice, 0.163; with practice setting, 0.982, with a graduate program,
0.31; and with sexual orientation, 0.788. The statistically insignificant results indicate
that appearing poised is not related to demographic traits.

115
For Question 13, lacking respect and feeling intolerant, the p value with gender
was 0.126; with strength of religion, 0.462; with age, 0.6; with years of practice, 0.473;
with practice setting, 0.922, with a graduate program, 0.57; and with sexual orientation,
0.783. The statistically insignificant results indicate that this variable does not associate
with demographic characteristics. Concerning Question 14, feel comfortable working
with clients’ sexual issues and concerns, the p value with gender was 0.319; with strength
of religion, 0.972; with age, 0.457; with years of practice, 0.155; with practice setting,
0.289, with a graduate program, 0.382; and with sexual orientation, 0.362. As such, the
statistically insignificant results demonstrate that the null hypothesis of distribution
independence cannot be rejected.
In summary, for the comfort, variable-based questions, a therapist communicating
effectively about sexuality may be related to age and years of practice. Additionally, how
unconcerned a therapist is about influencing a client’s sexuality may be associated with
years of experience in their occupation. For other questions, a statistically significant
association was not found.
H06 stated that there is no statistically significant relationship between the
independent variables of a therapist’s age, sex, sexual orientation, number of years in
practice, type of a graduate program, relationship status, practice setting, or strength of
religion and the dependent variable of a therapist’s willingness to discuss sexual topics.
There was a significant relationship between a therapist’s practice setting and a
therapist’s willingness to discuss sexual topics, r(88) = .22, p = .036, two-tailed.
However, there were no other significant relationships as determined by the Pearson’s r.

116
Fisher’s exact test did find two statistically significant relationships, with age, p = .022
and years of practice, p = .02 showing significance compared with responding openly and
confidently when sexual values are challenged. Also, years of practice, p = .012, was
significant with being unconcerned about influencing a client’s sexuality. Therefore, the
null hypothesis was partially rejected. The hypotheses and outcomes are summarized in
Table 13.

117
Table 13
Hypothesis Summary and Outcomes
Hypothesis
Statistical
test
Significance
Outcome
H01: There is no statistically significant relationship
between the independent variables (attitudes,
knowledge, training, supervision experience, and
clinical experience) and a therapist’s willingness to
discuss sexual topics with clients.
Pearson’s r
p values ranged
from .002 to .819
Null
partially
rejected
H02: There is no statistically significant relationship
between the independent variables (attitudes,
knowledge, training, supervision experience, and
clinical experience) and a therapist’s comfort
discussing sexual topics with clients.
Pearson’s r
p values ranged
from .078 to .931
Null
accepted
H03: There is no statistically significant predictive
relationship between the independent variables
(attitudes, knowledge, training, supervision
experience, and clinical experience) and a therapist’s
comfort level with sexuality.
Stepwise
multiple
linear
regression
No model
generated
Null
accepted
H04: There is no statistically significant predictive
relationship between the independent variables
(attitudes, knowledge, training, supervision
experience, and clinical experience) and a therapist’s
willingness to discuss sexual topics with clients.
Stepwise
multiple
linear
regression
p < .001 for
model, but only
two variables
were included
Null
partially
rejected
H05: There is no statistically significant relationship
between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in
practice, type of graduate program, relationship
status, practice setting, or strength of religion and the
dependent variable of sexual comfort of a therapist.
Pearson’s r
Fishers exact
test
p values ranged
from .385 to .894
p values ranged
from .05 to .995
Null
accepted
Null
partially
rejected
H06: There is no statistically significant relationship
between the independent variables of a therapist’s
age, sex, sexual orientation, number of years in
practice, type of graduate program, relationship
status, practice setting, or strength of religion and the
dependent variable of a therapist’s willingness to
discuss sexual topics.
Pearson’s r
Fishers exact
test
p values ranged
from .036 to .967.
p values ranged
from .012 to .972
Null
partially
rejected
Null
partially
rejected

118
Conclusions
Six research questions and six related hypotheses were originated for
investigation. Statistical analyses included the Pearson’s r, stepwise multiple linear
regression, and the Fisher’s exact test. The Pearson’s r calculation determined that there
was a significant, positive relationship between graduate sexuality training and a
therapist’s willingness to discuss sexual topics. There was a significant, positive
relationship between supervision experience and a therapist’s willingness to discuss
sexual topics. There was a significant, positive relationship between clinical experience
and a therapist’s willingness to discuss sexual topics.
When examined collectively by stepwise multiple linear regression from the
following independent variables, attitudes, knowledge, training, supervision experience,
and clinical experience, I determined that clinical experience and supervision experience
were the two variables that predicted a therapist’s willingness to discuss sexual topics
with clients respectively and accounted for 18% of the variance in a therapist’s
willingness to discuss sexual topics with clients. The Pearson’s r determined that there
was a significant relationship between a therapist’s practice setting and a therapist’s
willingness to discuss sexual topics. The coding of the variable for practice setting means
that therapists who are willing to discuss sexual topics are more likely to be in private
practice than in other settings. Fisher’s exact test determined there was a significant
relationship between gender and willingness to discuss sexual abuse, a significant
relationship between age and years of practice, and responding openly and confidently
when sexual values are challenged. Also, Fisher’s exact test found that there was a

119
statistically significant relationship between years of practice and how unconcerned a
therapist is about influencing a client’s sexuality. Implications are discussed in Chapter 5.

120
Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of this quantitative cross-sectional study was to measure the
relationships between marriage and family therapists’ attitudes, knowledge, supervision
experience, clinical experience, and graduate training and the dependent variables of
comfort while discussing sexual topics and willingness to discuss topics regarding
sexuality with clients. A secondary objective of this study was to assess how age,
religion, sexual orientation, gender, and practice setting affected therapists’ willingness to
discuss sexual topics with clients and therapists’ comfort levels while engaging clients a
in discussion about their sexual issues.
The first finding was a statistically significant relationship between graduate
sexuality training and a therapist’s willingness to discuss sexual topics with a client as
determined by the Pearson’s r correlation test. The stepwise linear regression analysis
indicated a statistically significant relationship between supervision experience and a
therapist’s willingness to discuss sexual topics with a client. A unique finding not
previously reported in the literature was a statistically significant relationship between
clinical supervision and a therapist’s willingness to discuss sexual topics with a client.
The two variables of supervision experience and clinical experience combined to account
for 18% of the variance in a therapist’s willingness to discuss sexual topics with a client.
There was a significant relationship between a therapist’s practice setting and a
therapist’s willingness to discuss sexual topics with a client.
In addition, Fisher’s exact test results indicated a statistically significant
relationship (p = 0.05) between gender and a therapist’s willingness to discuss sexual

121
topics with clients and regarding a therapist’s comfort in discussing sexual topics. I found
statistically significant results for age and years in practice. The results of this study
helped to fill in the gap in the literature by continuing the work that Harris and Hays
(2008) started and Cupit (2010) continued. Although Cupit’s findings were limited to
counselors, the findings are relevant to the marriage and family therapy community. The
instruments used in this study were predominantly drawn from Harris and Hays’s study
with a few modifications.
Interpretation of the Findings
The available literature was sparse regarding examination of the independent
variables that correlated to a willingness to discuss sexual topics with clients and the
comfort of the therapist while engaging in a discussion with the client. This gap in the
literature (see Cupit, 2010; Decker, 2010; Dermer & Bachenberg, 2015; Dunk, 2007;
LoFrisco, 2013; Yelton & Delfin, 2013) prompted the current study. The first finding was
a significant positive correlation between graduate sexuality training and a therapist’s
willingness to discuss sexual topics, r(88) = .31, p = .003, two-tailed, coefficient of
determination (r2) = .0961. The more graduate sexuality training a therapist had, the more
likely the therapist would be willing to discuss a sexual topic with a client. The graduate
sexuality training variable accounted for 9.61% of the variance in a therapist’s
willingness to discuss sexual topics with a client. This finding was consistent with what
Harris and Hays (2008) found that the more graduate-level sexuality-specific training
therapists received, the more willing they were to initiate a conversation with clients
about their sexual health. This finding was also consistent with the finding by Donovan

122
(2011), which was that graduate training had a strong correlation with the willingness to
initiate a conversation with a client, with t(84) = 2.016, p = .047, two-tailed. Donovan’s
study also included 90 participants who were social workers and therapists who had a
master’s in social work. Donovan concluded that “this indicates that those with human
sexuality training are more likely to initiate sexuality-related discussions with their
clients than those without training” (p. 43). Cupit (2010) also found that graduate
specializations affected therapists’ willingness to discuss sexual topics with clients.
Cupit’s finding that human sexuality training and education were statistically significant
(r = .26, p < .01) as a predictor variable in a regression analysis supported the finding
from the current study that the more graduate sexuality training therapists have, the more
likely they will be to discuss sexuality with clients.
The next finding was a significant positive correlation between supervision
experience and a therapist’s willingness to discuss sexual topics, r(88) = .32, p = .002,
two-tailed, with the coefficient determination (r2) = .1024. Findings indicated that
10.24% of the overall variance in a therapist’s willingness to discuss sexual topics with a
client could be explained by the supervision experience that the therapist had received.
Harris and Hays (2008) found that supervision experience was the second highest
predictor of a therapist’s willingness to discuss a sexual topic with a client, with indirect
effects (r = .17) and direct effects (r = .20) being statistically significant. Decker (2010)
found that the more supervision experience therapists received, the more likely they were
to initiate a conversation with a client regarding their sexual health. Cupit (2010) also
found a statistically significant relationship between supervision experience and a

123
therapist’s willingness to discuss sexual issues with a client with the results being r = .38,
p < .01. Cupit found that 14% of the variance could be explained by supervision
experience, (r2) = .14, which was similar to the present study’s finding. Given the
alignment between Harris and Hays, Cupit, and Decker, supervision experience is an
important factor influencing a therapist’s willingness to discuss sexual topics.
The last finding from the current study was that clinical experience showed a
significant positive correlation with a therapist’s willingness to discuss sexual topics,
r(88) = .32, p = .002, two-tailed, with the coefficient determination (r2) = .1024. Findings
indicated that 10.24% of the overall variance in a therapist’s willingness to discuss sexual
topics with clients is explained by the supervision experience that the therapist had
received. Harris and Hays (2008) did not find a significant relationship between clinical
experience and a therapist’s willingness to discuss sexual topics but noted that the
relationship was close to being statistically significant with p = .08. This result was the
same as what Hays (2002) had found earlier. Therefore, it is reasonable to conclude that
clinical experience has a statistically significant relationship with a therapist’s willingness
to discuss sexual topics. Decker (2010) found that clinical experience was an important
component of a therapist’s willingness to discuss sexual topics and should be combined
with supervision to prepare therapists to initiate discussions. Donovan (2011) echoed this
finding by noting that the more hands-on experience therapists have while in school, the
more likely they will be to initiate a discussion with a client about the client’s sexual
well-being. Cupit (2010) did not find a relationship between clinical experience and a
willingness to discuss sexual topics with a client. Harris and Hays pointed out that the

124
reason clinical experience was impactful was that their study focused on practicing
therapists, whereas other studies had focused on students who may not have had
significant clinical experience. There was no other plausible reason I could find for this
discrepancy between the study findings.
The present study did not indicate significant relationships between sexual
attitudes, knowledge, training, supervision experience, or clinical experience and
comfort. These findings contrasted with those from other major studies. The reason may
have been the smaller sample size. However, the size of the current study sample (N =
90) was similar to that used by other researchers, LoFrisco (2013) had 57 participants,
Decker (2010) had 103 participants, and Donovan (2011) had 90 participants. The one
relationship that came close to having statistical significance was sexual attitudes
(permissiveness) with p = .079. This was consistent with Cupit’s (2010) finding of only
one small correlation between attitude (communion) and comfort. Cupit had a larger
sample than the present study. The current findings contradicted what other researchers
had found, which indicated that knowledge, supervision, and attitudes have the greatest
impact on comfort (see Donovan, 2011; Cupit, 2010; M. S. Green et al., 2009; Harris &
Hays, 2008; Juergens et al., 2009). This discrepancy may be due to the smaller sample
size. However, because of the limited amount of research done in this area, it is difficult
to explain the discrepancy in findings.
The first statistically significant finding from the stepwise linear regression
analysis was that clinical experience predicted willingness to discuss sexual topics with a
client (β = 0.28, t = 2.81, p = .006). The second statistically significant finding was that

125
supervision experience predicted willingness to discuss sexual topics with a client (β =
0.27, t = 2.77, p = .007). The regression model indicated F(2, 87) = 9.28, p < .001; R2
= .18, compares with what Cupit (2010) found using the same variables, F=18.20, p
< .01, R2 =.163. Cupit found that supervision experience was a predictor variable of
statistical significance with β = 0.380 and R2 = .144. This was consistent with what I
found. However, Cupit found that sexual attitude regarding birth control was the
secondary predictor with β = -.137 and R2 = .163. The present study indicated that clinical
experience was the secondary predictor variable.
The first statistically significant finding from the Fisher’s exact test was that
gender significantly relates to a willingness to discuss sexual abuse, p = .05. This was a
weak correlation, but it was consistent with findings from other studies, namely Decker
(2010) and Easton (2015). The second and third statistically significant findings from the
Fisher’s exact test were that age, p = .022, and years of practice, p = .02, relate to comfort
and responding openly and confidently when the client challenges sexual values. This
was consistent with what Decker and Træen and Schaller (2013) found: Older, more
experienced therapists were more comfortable and more willing to discuss sexual health
issues with clients.
The implications of this study derived from Bowenian theory were that
supervision experience (i.e., thoughtful instruction from trained professionals who have
the experience and the capacity to provide guidance and insight to supervisees coupled
with clinical experience) reduces the anxiety of initiating and discussing sexual topics.
The concept of knowledge needed to be divided into two components. First, there is the

126
knowledge derived from courses, books, and lectures, and second, there is the knowledge
derived from personal experience. Knowledge gained by the supervision and clinical
experience appears to lower anxiety because of the strong correlation between
supervision experience, clinical experience, and a willingness to discuss sexual topics
with clients. Graduate sexuality training combines coursework and field experience.
According to the Bowenian framework, one of the keys to reducing anxiety and
increasing the likelihood of establishing a healthy therapeutic alliance is receiving hands-
on experience in the field. Supervision is followed by clinical experience in which newly
acquired tools can be used; this process builds confidence in the therapist’s abilities,
thereby reducing anxiety and increasing the willingness to discuss sexual topics with
clients. The significant findings for supervision, clinical experience, and graduate
sexuality training were consistent with the findings from Harris and Hays’s (2008) study
and provide data for further research.
Limitations of the Study
In this study, there were several limitations. First, the findings may not be
generalizable to the overall therapist population because of the sample size. Also, the
skewed response rate, with a largely female participant base, also limited the usability of
the findings (see Field, 2013; Frankfort-Nachmias & Nachmias, 2008). The second
limitation was the instrument size. With over 80 questions, this survey had the potential
to be both intimidating and overwhelming to participants, which may have prompted a
high opt-out rate. I indicated in the instructions that the average time to complete the
survey was 15 minutes, but without incentives to offer, that may have been too much time

127
to commit. I also included the standard language that participants were free to leave at
any time. Another limitation of this study was its lack of funding: There is not much
funding for sexuality-focused research.
The quantitative correlational survey design also constituted a limitation. The
findings are limited to correlations and cannot be used to establish causation.
Additionally, findings could not provide the rich depth and background information that a
qualitative or mixed-methods study might have provided. This study may have been
limited by the influence of social desirability bias (see Larson & Bradshaw, 2017). Social
desirability bias may have influenced participants to choose answers they believed others
would find acceptable or would be in alignment with the community within which the
therapist resides. Also, social desirability bias may have influenced this study by
depriving the participants of the ability to explain their choices through a qualitative
component (see Larson & Bradshaw, 2017).
Recommendations
In line with these limitations, I recommend that future research be focused on four
specific areas. First, I recommend there be additional research on how attitudes impact a
therapist’s willingness to initiate and discuss sexual topics. While the present study did
not find any such link, Cupit (2010) did, and other studies have as well. Therefore, I
believe that more research should be done on this variable moving forward.
The second recommendation is for additional research on how supervision
impacts a therapist’s willingness to initiate and to discuss sexual topics. The present study
found there was a strong correlation as did LoFrisco’s (2013) dissertation, which found

128
there to be a strong statistical significance for improving therapists through supervision.
Therefore, I recommend more research in this area to understand better how this
experience can help improve a therapist’s abilities in this area, and through that process,
better inform and improve the supervision that students are receiving.
The third recommendation is further exploration of how graduate sexuality
training impacts therapists. As this study was limited to a few questions on point, a mixed
methods study would be beneficial to understand how graduate-level sexuality training
(i.e., fieldwork or clinical experience inside of a course), impacts a therapist’s willingness
to initiate and discuss sexual topics and his or her comfort levels while conversing with
the client.
The fourth and final recommendation is the development of a new sexual
knowledge instrument because the one used in the present study was over 45 years old. It
seems past time to develop a new instrument that can be used by researchers going
forward.
Implications
In the current study, I aimed to fill in the gap in the literature by contributing to
the existing body of knowledge by adding to the current information about what factors
impact therapists and their willingness to discuss sexual topics with clients and their
comfort during this process. One key contribution of this study was that it highlighted the
importance of supervision in the development of therapists. Harris and Hays (2008)
similarly found that this is important. In the future, universities and colleges that offer
master’s and doctoral programs in marriage and family therapy should increase the focus

129
on supervision as a means of enhancing a therapist’s willingness to discuss. As LoFrisco
(2013) pointed out, it is not the comfort of the therapist that is of paramount importance.
Rather, it is the willingness of the therapist and the comfort of the client that should be
the focus.
The second key contribution of this study that dovetails with the supervision
element was the clinical experience factor, and how it has a strong correlation with a
willingness to discuss sexual topics. Again, this is in line with what Harris and Hays
(2008) found; it is important for future therapists to acquire sufficient clinical experience
in dealing with sexual issues before graduation given how important sexuality is and how
challenging a topic it can be to discuss.
I will disseminate the key findings from this study through my WordPress website
to the marriage and family therapist community. This will assist the general community
in informing what variables are statistically significant and strongly correlate with a
willingness to discuss sexual issues and may aid in the increase of skill sets of therapists
through attendance at workshops or local graduate courses focused on this particular area
of study. Through the sharing of these findings, I hope to increase the attention that this
area receives inside of the marriage and family therapy community and highlight that this
continues to be an ongoing issue. Our communities thrive when individuals are healthy,
happy, and balanced; this can only be achieved by receiving quality therapy that is
attuned to the client’s needs. The results of this will serve to add information for
educators as they shape the curriculum and clinicals to better prepare therapists to deal
with discussing sexuality with their clients.

130
Conclusion
There is a dearth of literature on the topic of therapists and their willingness to
discuss sexual topics with clients. At present, there are only two studies, this one and
Harris and Hays’s (2008) that have addressed this issue. Therapists as a whole are still
uncomfortable discussing sexual topics with clients (Dermer & Bachenberg, 2015). The
lack of comfort is prevalent among early practitioners (Timm, 2009). The present study
found that age and years of practice had a statistically significant relationship with
comfort. Given that there was a strong correlation between supervision experience and
willingness to discuss sexual topics and a strong correlation between clinical experience
and willingness to discuss, it seems appropriate to draw the conclusion that, with
extensive hands-on experience combined with years of practice experience and age, a
therapist can have a level of comfort while discussing sexual topics. When one takes a
step back and looks at the findings of this study, the overall conclusion is that several
factors make a therapist more willing to step outside of their comfort zone and engage the
client in a discussion about a sexual topic. Comfort comes after years of practice; comfort
comes with willingness. The factors that underpin this process are the combination of
direct supervision, clinical experience, and graduate training focused on sexuality. These
taken together are what makes up a therapist’s knowledge and experience and has the
strongest correlation to increasing a therapist’s willingness to discuss sexuality with a
client.
I believe moving forward that the marriage and family therapy community needs
to be comfortable with discussing sexual topics with clients; even more than that, I want

131
every therapist to be willing, despite any lack of comfort, to initiate the conversation.
Educational institutions must be more aware of this need and look to fill it through
requirements of coursework that provide sexuality-specific clinicals focused on dealing
with sexual issues and supervision by therapists who are experienced and knowledgeable
in this area. This will help address the needs of the clients in our respective communities
and bring about positive social change as a result through having individuals whose needs
are being met by marriage and family therapists.

132
References
Alessi, E. J., Dillon, F. R., & Kim, H. M. S. (2015). Therapist correlates of attitudes
toward sexual minority individuals, affirmative counseling self-efficacy, and
beliefs about affirmative practice. Psychotherapy Research, 26(4), 1–13.
https://doi.org/10.1080/10503307.2015.1026422
Alessi, E. J., Dillon, F. R., & Kim, H. M. S. (2015). Therapist correlates of attitudes
toward sexual minority individuals, affirmative counseling self-efficacy, and
beliefs about affirmative practice. Psychotherapy Research, 26(4), 1–13.
https://doi.org/ 10.1080/10503307.2015.1026422
American Psychiatric Association. (2013). Diagnostic and statistical manual of mental
disorders (5th ed.). Arlington, VA: American Psychiatric Publishing.
Anderson, M. J. (2002). Counselor comfort with sexual issues (Unpublished doctoral
dissertation). University of New Orleans, New Orleans, LA.
Andrews, W. C. (2000). Approaches to taking a sexual history. Journal of Women’s
Health & Gender-Based Medicine, 9(1), 21–24.
https://doi.org/10.1089/152460900318821
Arikan, F., Meydanlioglu, A., Ozcan, K., & Ozer, Z. C. (2015). Attitudes and beliefs of
nurses regarding discussion of sexual concerns of patients during
hospitalization. Sexuality and Disability, 33(3), 327–337. Retrieved from
https://link.springer.com/journal/11195
Baer, B. E., & Murdock, N. L. (1995). Non-erotic dual relationships between therapists
and clients: The effects of sex, theoretical orientation, and interpersonal

133
boundaries. Ethics & Behavior, 5(2), 131–145.
https://doi.org/10.1207/s15327019eb0502_2
Bal, M. D., & Sahiner, N. C. (2015). Turkish nursing students’ attitudes and beliefs
regarding sexual health. Sexuality and Disability, 33(2), 223–231.
https://doi.org/10.1007/s1119
Bancroft, J. (2009a). Human sexuality and its problems. London, England: Churchill
Livingstone/Elsevier.
Bancroft, J. (2009b). Sex therapy needs building not deconstruction. Archives of Sexual
Behavior, 38, 1028–1030. Retrieved from
https://kinseyinstitute.org/pdf/Bancroft%20ASB%202009.pdf
Banwari, G., Mistry, K., Soni, A., Parikh, N., & Gandhi, H. (2015). Medical students and
interns’ knowledge about and attitude toward homosexuality. Journal of
Postgraduate Medicine, 61(2), 95. https://doi.org/10.4103/0022-3859.153103
Bowen, M. (1976). Theory in the practice of psychotherapy. Family Therapy: Theory and
Practice, 4(1), 2–90. Retrieved from
http://www.cflarchives.org/images/TheoryInThePractice.pdf
Burch, A. (2005). Health care providers’ knowledge, attitudes, and self-efficacy for
working with spinal cord injured patients with diverse sexual orientations
(Doctoral dissertation). Retrieved from ProQuest Dissertations and Theses
database (Order No. 3175668).
Byrne, M., Doherty, S., McGee, H. M., & Murphy, A. W. (2010). General practitioner
views about discussing sexual issues with patients with coronary heart disease: A

134
national survey in Ireland. BMC Family Practice, 11(1), 40.
https://doi.org/10.1186/1471-2296-11-40
Campbell, D. T., & Stanley, J. C. (1966). Experimental and quasi-experimental designs
for research. Chicago, IL: Rand McNally.
Carlson, M. D., & Morrison, R. S. (2009). Study design, precision, and validity in
observational studies. Journal of Palliative Medicine, 12(1), 77–82.
https://doi.org/10.1089/jpm.2008.9690
Chapman, R., Watkins, R., Zappia, T., Nicol, P., & Shields, L. (2012). Nursing and
medical students’ attitude, knowledge and beliefs regarding lesbian, gay, bisexual
and transgender parents seeking health care for their children. Journal of Clinical
Nursing, 21(7–8), 938–945. https://doi.org/10.1111/j.1365-2702.2011.03892.x
Cohen, L., Manion, L., & Morrison, K. (2007). Research methods in education (6th ed.).
London, England: RoutledgeFalmer.
Conrad, C., & Serlin, R. C. (2005). The Sage handbook for research in education:
Engaging ideas and enriching inquiry. Thousand Oaks, CA: Sage.
Cort, E. M., Attenborough, J., & Watson, J. P. (2001). An initial exploration of
community mental health nurses’ attitudes to and experience of sexuality-related
issues in their work with people experiencing mental health problems. Journal of
Psychiatric and Mental Health Nursing, 8(6), 489–499.
https://doi.org/10.1046/j.1351-0126.2001.00425.x
Creswell, J. W. (2009). Research design: Qualitative, quantitative, and mixed methods
approaches (Laureate Education, Custom Ed.). Thousand Oaks, CA: Sage.

135
Creswell, J. W. (2013). Research design: Qualitative, quantitative, and mixed methods
approaches (4th ed.) Los Angeles, CA: Sage.
Cupit, R. W. (2010. Counselors' comfort levels and willingness to discuss sexual issues
with couples they counsel (Doctoral dissertation). Retrieved from ProQuest
Dissertations and Theses database (Order No. 3414807).
Cushing, A., Evans, D., & Hall, A. (2005). Medical students’ attitudes and behaviour
toward sexual health interviewing: Short- and long-term evaluation of designated
workshops. Medical Teacher, 27(5), 422–428.
https://doi.org/10.1080/01421590500046502
Decker, D. M. (2010). Clinical supervision of marriage and family therapists and
addressing the sexual needs of clients: A preliminary investigation (Doctoral
dissertation). Retrieved from ProQuest Dissertations and Theses database (Order
No. 3418816).
Dermer, S., & Bachenberg, M. (2015). The importance of training marital, couple, and
family therapists in sexual health. Australian and New Zealand Journal of Family
Therapy, 36(4), 492–503. https://doi.org/10.1002/anzf.1122
Diamond, L. M., & Huebner, D. M. (2012). Is good sex good for you? Rethinking
sexuality and health. Social and Personality Psychology Compass, 6(1), 54–69.
https://doi.org/10.1111/j.1751-9004.2011.00408.x
Dixon-Woods, M., Regan, J., Robertson, N., Young, B., Cordel, C., & Tobin, M. (2002).
Teaching and learning about human sexuality in undergraduate medical education.

136
Medical Education, 36(5), 432–440. https://doi.org/10.1046/j.1365-
2923.2002.01198.x
Doll, G. M. (2013). Sexuality in nursing homes: Practice and policy. Journal of
Gerontological Nursing, 39(7), 30–37. https://doi.org/10.3928/00989134-
20130418-01
Donovan, C. (2011). Examining the relationship between human sexuality training and
therapist comfort addressing sexuality with clients (Unpublished master’s thesis).
Smith College, Northampton, MA.
Dunk, P. (2007). Everyday sexuality and social work: Locating sexuality in professional
practice and education. Social Work and Society, 5(2), 135–142. Retrieved from
http://www.socwork.net/sws/article/view/112/401
Dyer, K., & das Nair, R. (2013). Why don’t healthcare professionals talk about sex? A
systematic review of recent qualitative studies conducted in the United
Kingdom. The Journal of Sexual Medicine, 10(11), 2658–2670. https://doi.org
10.1111/j.1743-6109.2012.02856.x
Easton, A. B. (2015). Certified rehabilitation counselors’ willingness to address
sexuality-related concerns with clients with autism spectrum disorder (Doctoral
dissertation). Retrieved from ProQuest Dissertations and Theses database (Order
No. 3715686)
Edmondson, A. C., & McManus, S. E. (2007). Methodological fit in management field
research. Academy of Management Review, 32(4), 1246–1264. Retrieved from
https://www.cebma.org/wp-content/uploads/Edmondson-and-McManus-2007-.pdf

137
Eliason, M., DeJoseph, J., Dibble, S., Deevey, S., & Chinn, P. (2011). Lesbian, gay,
bisexual, transgender, and queer/questioning nurses’ experiences in the
workplace. Journal of Professional Nursing, 27(4), 237–244.
https://doi.org/10.1016/j.profnurs.2011.03.003
Farmer, L. B., Welfare, L. E., & Burge, P. L. (2013). Counselor competence with lesbian,
gay, and bisexual clients: Differences among practice settings. Journal of
Multicultural Counseling & Development, 41(4), 194–209.
https://doi.org/10.1002/j.2161-1912.2013.00036.x
Field, A. (2013). Discovering statistics using IBM SPSS statistics and sex and drugs and
rock ‘n’ roll. Los Angeles, CA: Sage.
Flaget-Greener, M., Gonzalez, C. A., & Sprankle, E. (2015). Are sociodemographic
characteristics, education and training, and attitudes toward older adults’ sexuality
predictive of willingness to assess sexual health in a sample of US
psychologists? Sexual and Relationship Therapy, 30(1), 10–24.
https://doi.org/10.1080/14681994.2014.948297
Ford, M. P., & Hendrick, S. S. (2003). Therapists’ sexual values for self and clients:
Implications for practice and training. Professional Psychology: Research and
Practice, 34, 80–87. https://doi.org/10.1037/0735-7028.34.1.80
Frankfort-Nachmias, C., & Nachmias, D. (2008). Research designs: Cross-sectional and
quasi-experimental designs. In C. Frankfort-Nachmias, D. Nachmias, & J.
DeWaard (Eds.), Research methods in the social sciences (7th ed.) pp. 184–216.
New York, NY.: Worth.

