


Running Head: PATHOPHYSIOLOGY OF ASTHMA 1
Pathophysiology of asthma
Human Physiology BIOM 525-D05
Dr. Jonathan Moreno
April 18, 2021
Liberty University
Introduction

Running Head: PATHOPHYSIOLOGY OF ASTHMA 2
Asthma is a quite common disease in our population. This disease is
characterized by symptoms that include tightness of chest, shortness of breath, cough,
and most notably wheezing. These symptoms are caused by chronic airway
inflammation that leads to airway hyperresponsiveness and expiratory airflow limitation
in various degrees (Prakash, 2020). This disease impacts the function of the respiratory
system. The function of the respiratory system is the exchange of oxygen and carbon
dioxide between the body and the environment (Costanzo, 2018). Asthma then interference
with the normal process of air exchange between these two entities causing a disease
state.
This paper will review the pathophysiology of asthma delving into the
epidemiology and etiology of the disease. It will go over the EPR-3 classification of
asthma which divides it into four groups: intermittent, persistent-mild, persistent-
moderate, and persistent-severe. The molecular basis of the disease verses the normal
physiology and homeostasis of the respiratory system. The disease has unique
laboratory findings which can help with diagnosis and treatment. Lastly, a review of
complication that can occur in asthma and the prognosis of the disease.
Epidemiology
Asthma is a heterogeneous clinical syndrome that affects all age groups, yet
most common impacting children worldwide (Stern, Pier, & Litonjua, 2020). “The National
Asthma and Education and Prevention Program Expert Panel Report 3 (NAEPPR3)
defines asthma as a chronic inflammatory disorder of the airways in which many cells
and cellular elements play a role” (Stern, Pier, & Litonjua, 2020). Asthma prevalence data in
the United States has been obtained by national surveys with the most recent data

Running Head: PATHOPHYSIOLOGY OF ASTHMA 3
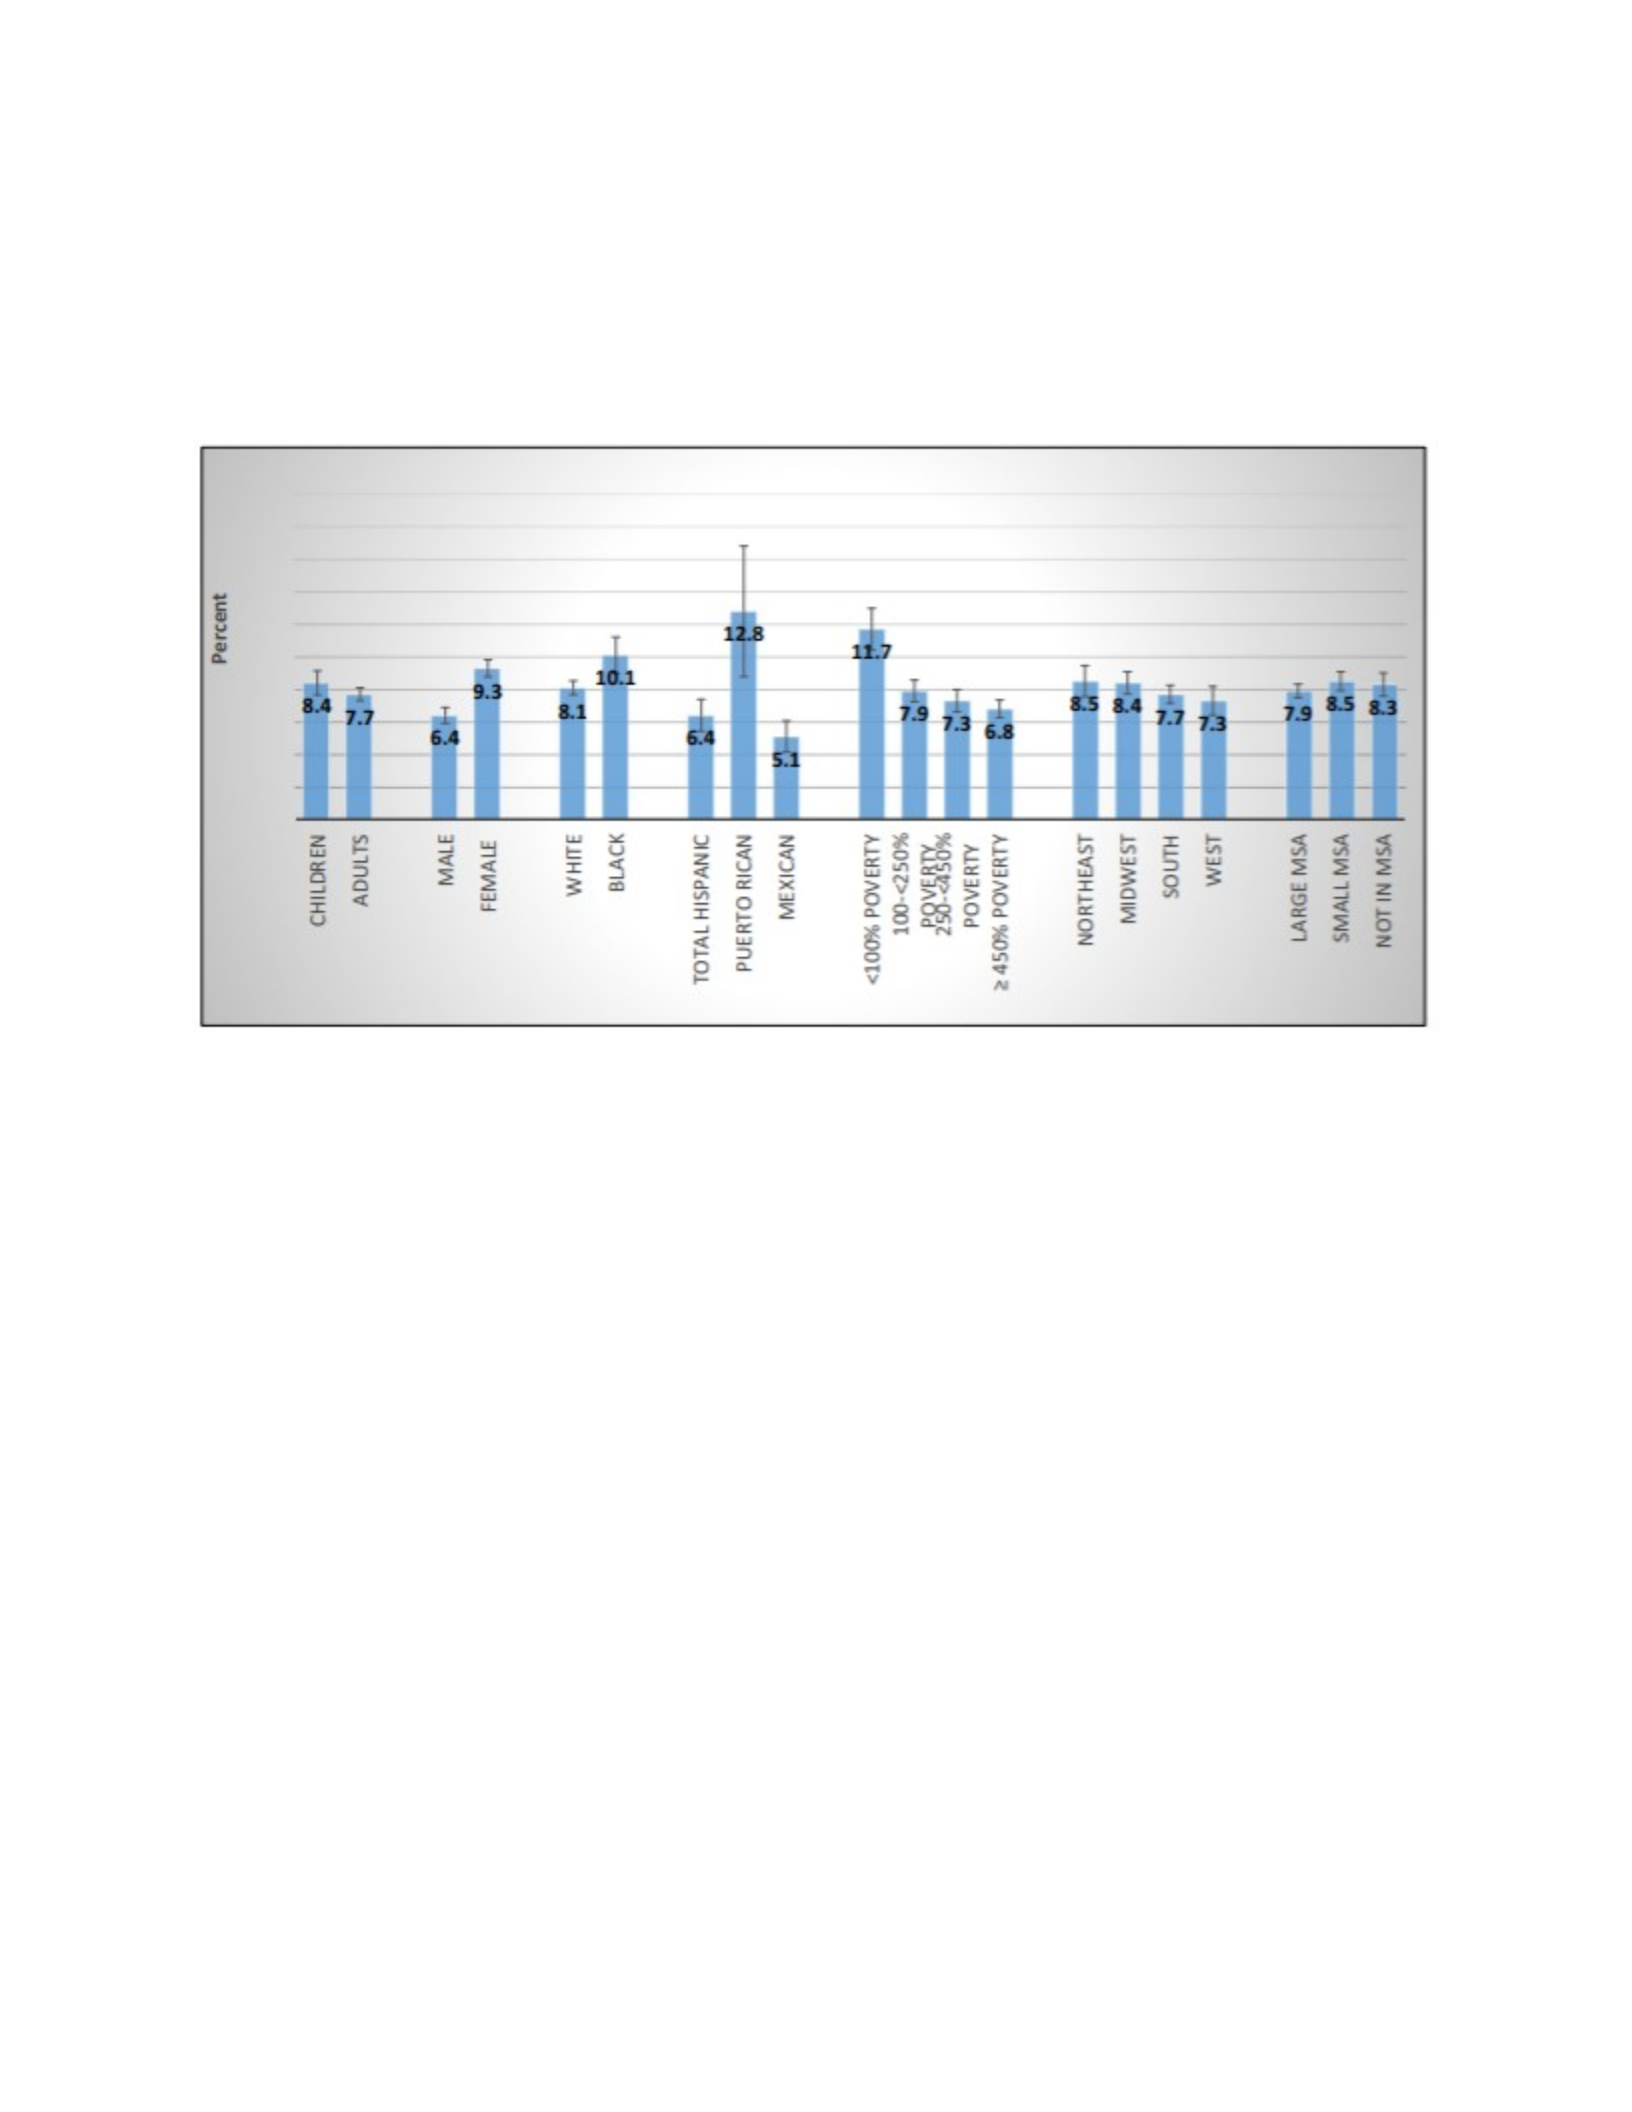
coming from the Centers for Disease Control and Prevention (CDC). In 2017 a 7.9%
prevalence of asthma in the USA was recorded. Children (<18 years) had a higher rate
at 8.4% than in adults at 7,7% (Stern, Pier, & Litonjua, 2020). There is an estimated 241
million people in the world that suffer from asthma (Stern, Pier, & Litonjua, 2020).
Asthma is considered the most common chronic disease responsible for
morbidity and mortality. Asthma prevalence can also vary by several other variables
such as sex, race, ethnicity, poverty status, region, and residence as seen in figure 1
(Stern, Pier, & Litonjua, 2020). A study conducted by the Epidemiology and Natural History
of Asthma called, outcomes and treatment regimens (TENOR I and TENOR II)
demonstrated the high morbidity in patients with severe and difficult to treat asthma
(Haselkorn PhD, et al., 2018). In this study it was shown that the level of asthma control has
changed minimally through the years despite using standard of care therapy (Haselkorn
PhD, et al., 2018).
Etiology
Asthma differs in etiology which comprises a range of heterogeneous
phenotypes (Subbarao, Mandhane, & Sears, 2009). The risk factors for asthma are genetics,
environmental factors, and host factors (Subbarao, Mandhane, & Sears, 2009). While family
history can be documented it is not sufficient or needed to develop asthma (Subbarao,
Mandhane, & Sears, 2009). There has been a substantial increase in the incidence of
asthma with evidence supporting that environmental changes have a big impact in the
asthma epidemic (Subbarao, Mandhane, & Sears, 2009). These environmental triggers impact
the asthma differently in a person’s life changing the relevant risk factors (Subbarao,
Mandhane, & Sears, 2009).

Running Head: PATHOPHYSIOLOGY OF ASTHMA 4
The risk factor of genes has been studied and 18 genomic regions and more
than 100 genes have been linked with asthma and allergies in different populations
(Subbarao, Mandhane, & Sears, 2009). A second, prenatal risk factors such as prenatal
tobacco smoke has been consistently associated with wheezing and decrease airway
calibre during childhood (Subbarao, Mandhane, & Sears, 2009). A third risk factor observed is
prenatal nutrient levels and dietary interventions that have focused on foods with anti-
inflammatory properties and antioxidants like vitamin E and zinc (Subbarao, Mandhane, &
Sears, 2009). High levels of vitamins E, zinc, and consumption of fish have been shown to
decrease the development of wheezing in children up to five years old (Subbarao,
Mandhane, & Sears, 2009).
Types/Classification
The National Asthma Education and Prevention Program created a guideline in
2007 titled Expert Panel Report 3 (EPR-3) to help in diagnosis and management of
asthma. The approach presented in the guideline allows a subjective evaluation based
on an individual patient’s daily activities, work environments, and home or family
environments (Pollart MD & Elward MD, 2009). The EPR-3 guideline divides asthma severity
into four groups; intermittent, persistent-mild, persistent-moderate, and persistent-
severe (Pollart MD & Elward MD, 2009). These classifications focus on key elements of
monitoring and assessment which focus on severity, control and responsiveness to
treatment (Pollart MD & Elward MD, 2009).
Normal Physiology and Homeostasis

Running Head: PATHOPHYSIOLOGY OF ASTHMA 5
When it comes to respiration the primary organ are the lungs which take in
oxygen and expel carbon dioxide during breathing. When we inhale a gas exchange
occurs buy first getting filtered in the throat, trachea, or windpipe. The trachea leads to
the lungs where oxygen is moved into the bloodstream. A pressure gradient between
the atmosphere and the alveoli drives the airflow into and out of the lung (Costanzo, 2018).
This airflow is directly proportional to the difference in pressure between the alveoli and
mouth. Airflow is also inversely proportional to airway resistance (Costanzo, 2018). The
relaxation and contraction of bronchial smooth muscle changes the radius of the
airways which in turn changes airway resistance (Costanzo, 2018). B2-adrenergic
receptors dilate the airway when stimulated (Costanzo, 2018). Cholinergic muscarinic
receptors constrict the airways (Costanzo, 2018). During homeostasis of respiration the
forced expiratory volume (the volume of air that can be expired in the first second of a
forced expiration) is normally 80% of the forced vital capacity (Costanzo, 2018). Forced
vital capacity is the volume of air that can be expired after inspiration (Costanzo, 2018). In
asthma both forced vital capacity and forced expiratory volume is reduced (Costanzo,
2018).
Pathophysiology and Molecular Basis of Asthma
Asthma that is induced by eosinophils can be seen to have a 50 to 100 fold
increase in the numbers in relation to neutrophils in the bronchial mucosa (Wardlaw,
1999). This increase is not based on a single molecular event but the sequential effect in
bone marrow by mediated IL-5 (increases circulating eosinophils), selection of
eosinophils to venular endothelium through P-selection, P-selectin glycoprotein ligand 1,
activation antigen-4, and vascular cell adhesion molecule-1 (Wardlaw, 1999). In asthma,

Running Head: PATHOPHYSIOLOGY OF ASTHMA 6
the airways receive a trigger such as dust, this trigger causes inflammation of the
smooth muscle that surrounds the airway lumen (Costanzo, 2018). This inflammation
causes contraction of the muscle which leads to the lumen getting smaller. This causes
an asthma attack by limiting the air to excel from the lungs. In Addition, the goblet cells
surrounding the muscle release mucus into the lumen (Maddox & Schwartz, 2002). This
inflammation can be caused by elevated IgE levels (Maddox & Schwartz, 2002). This is an
immunoglobulin that causes a cascade of events through an increase of basophils and
mast cells in the lamina propria which release histamine (Maddox & Schwartz, 2002). This
Histamine causes swelling of the airways.
Beta and muscarinic receptors are the two types of receptors that are released in the
smooth muscle. The Beta receptor causes muscle relaxation, and the muscarinic
receptor causes constriction (Maddox & Schwartz, 2002). In Asthma, the treatment is geared
towards blocking the muscarinic receptors and activating the beta receptors. Therefore,
antimuscarinic and Beta agonist drugs are used as treatment. Also, the inflammation
which causes constriction of the smooth muscle is treated with anti-inflammatory drugs
(Maddox & Schwartz, 2002).
Signs and Symptoms:
The signs and symptoms of asthma include persistent cough, chest tightness,
wheezing during expiration, and difficulty breathing (Zhengguang, et al., 2020). Other signs
and symptoms in more severe patients include bronchial hyper-responsiveness, nasal
congestion, exercise induced bronchoconstriction, sleep disturbances, and nasal
congestion (Zhengguang, et al., 2020). Now, an asthma attack can have more severe

Running Head: PATHOPHYSIOLOGY OF ASTHMA 7
symptoms such as bluish discoloration of the lips, a rapid pulse, flared nostrils and
pursed lips, sweating and extreme shortness of breath (Zhengguang, et al., 2020). These
symptoms tend to flare up depending on patient’s triggers.
Laboratory Features
There are several tests that can test for severity of oxygenation in the blood
which can be a blood gas test. This will give PO2 and PCO2 levels in the blood. Yet in
order to diagnosis asthma test such as an Eosinophil count of 3.2 % +-2.1 can be
beneficial in pinpointing the type of asthma (Adriano Queiroz, Rodrigues Fonseca, de Re, &
Maurici, 2021). These tend to correlate well with allergies. A Pulmonary function test can
also help in identifying asthma in a patient. While these tests can assist the major ones
are patient history and symptoms of wheezing and shortness of breath.
Differential Diagnosis:
There are many differential diagnosis of asthma, but some of the most common are
COPD, Pneumonia, Gastroesophageal reflux disease (GERD), and Congestive heart
failure(CHF). These conditions can all mimic asthma and should be examined further to
prevent overdiagnosis or underdiagnosis. For Example, Gastroesophageal reflux
disease (GERD) happens when contents in the stomach come up and irritate the
airway. This can cause symptoms of asthma such as cough, airway
hyperresponsiveness, and micro aspiration. “Reflux of gastric acid into the lower
esophagus may exacerbate asthmatic symptoms though vagally mediated
parasympathetic reflexes” (Slaughter, 2007). Nocturnal burning chest pain, dyspepsia and
throat clearing can differentiate GERD from asthma. Furthermore, treating GERD for a
few weeks will provide a clear diagnosis.

Running Head: PATHOPHYSIOLOGY OF ASTHMA 8
Complications and prognosis
Asthma is the most common respiratory disease worldwide and it’s on the rise. In
some patients, asthma can be accompanied by multiple comorbidities which can cause
further complications. These complications are the reason for many hospital emergency
visit (Covantev, Mazuruc, Uzdenov, & Corlateanu, 2019).
Whether Asthma is extrinsic (Atopic) or intrinsic (non-atopic), if not treated in a timely
manner, complications can be severe. Some of complications include persistent
tiredness, delay in growth or puberty (in Children), underperformance, psychological
problems such as stress, anxiety and depression (Covantev, Mazuruc, Uzdenov, & Corlateanu,
2019). Also, infections such as pneumonia. These asthma complications may be due to
lack of treatment compliance or overuse of the Asthma medications.G The Prognosis
depends on many factors such as adherence to therapy. Although it cannot be cured it
can be controlled to live a normal life. In some patients, there’s complete remission,
while others can have permanent lung damage. This can lead to more symptoms in
their daily life such as chronic cough and shortness of breath.
References

Running Head: PATHOPHYSIOLOGY OF ASTHMA 9
Adriano Queiroz, A. P., Rodrigues Fonseca, F., de Re, A., & Maurici, R. (2021). Clinical, laboratory, and
functional characteristics of asthma-COPD overlap in patients with a primary diagnosis of COPD.
Jornal brasileiro de pneumologia, 47(1), 1806. doi:10.36416/1806-3756/e20200033
Costanzo, L. S. (2018). Physiology. China: Elsevier.
Covantev, S., Mazuruc, N., Uzdenov, R., & Corlateanu, A. (2019). Spontaneous Pneumomediastinum- A
rare asthma complication. Folia Medica, 61(3), 472-477. doi:10.3897/folmed.61.e39419
Haselkorn PhD, T., Chipps MD, B. E., Paknis PharmD, B., Ortiz MD, B., Bleecker MD, E. R., Kianifard PhD,
F., . . . Zeiger MD, PhD, R. S. (2018). More than a decade follow up in patients with severe or
difficult to treat asthma. Journal of Allergy and Clinical Immunology, 141(5), 1590-1597.
doi:https://doi.org/10.1016/j.jaci.2017.07.014
Maddox, L., & Schwartz, D. A. (2002). The pathophysiology of asthma. Annual Review of Medicine, 53(1),
477. Retrieved from https://search-proquest-com.ezproxy.liberty.edu/docview/222628534?pq-
origsite=summon
Pollart MD, S. M., & Elward MD, K. (2009). Overview of changes to asthma guidelines: diagnosis and
screening. American Family Physician, 79(9), 761-767. Retrieved from
https://www.aafp.org/afp/2009/0501/p761.html#:~:text=The%20EPR%2D3%20guideline
%20classification,moderate%2C%20and%20persistent%2Dsevere.
Slaughter, M. C. (2007). Not quite asthma: differential diagnosis of dyspnea, cough, and wheezing.
Allergy and Asthma Proceedings, 28(3), 271-281. doi:10.2500/aap.2007.28.2995
Stern, J., Pier, J., & Litonjua, A. A. (2020, February ). Asthma epidemiology and risk factors. Seminars in
Innumopathology, 42(1), 5-15. doi:DOI:10.1007/s00281-020-00785-1
Subbarao, P., Mandhane, P. J., & Sears, M. R. (2009). Asthma: epidemiology, etiology and risk factors.
Canadian Medical Association Journal, 181(9), 181-190.
doi:https://doi.org/10.1503/cmaj.080612
Wardlaw, A. J. (1999). Molecular basis for selective eosionphil trafficking in asthma: A multistep
paradigm. Journal of Allergy and Clinical Immunology, 104(5), 917-926. doi:https://doi-
org.ezproxy.liberty.edu/10.1016/S0091-6749(99)70069-2
Zhengguang, H., Feng, J., Xia, J., Wu, Q., Yang, H., & Ma, Q. (2020). Frequency of signs and symptoms in
persons with asthma. Respiratory Care, 65(2), 252-264. doi:10.4187/respcare.06714
Running Head: PATHOPHYSIOLOGY OF ASTHMA 10
Figures
Figure 1 USA asthma prevalence stratified by age group, sex, race, ethnicity, poverty status,
geographic region, and place of residence. (Stern, Pier, & Litonjua, 2020)

