


MICROBIOLOGY FOR NURSING
To introduce the students to carbohydrate metabolism pathways at different levels in plants and
animals
INTRODUCTION
Metabolism is a highly coordinated cellular activity in which many multi-enzyme systems
(metabolic pathways) cooperate to:
(1) Obtain chemical energy by capturing solar energy or degrading energy rich nutrients
from the environment;
(2) Convert nutrient molecules into the cell’s own characteristic molecules, including
precursors of macromolecules;
(3) Polymerize monomeric precursors into macromolecules: proteins,nucleic acids, and
polysaccharides; and
(4) Synthesize and degrade biomolecules required for specialized cellular functions, such
as membrane lipids, intracellular messengers, and pigments.
Living organisms can be divided into two large groups according to the chemical form in
which they obtain carbon from the environment.
Autotrophs (such as photosynthetic bacteria, green algae, and vascular plants) can use carbon
dioxide from the atmosphere as their sole source of carbon, from which they construct all their
carbon-containing biomolecules. Some autotrophic organisms, such as cyanobacteria, can also
use atmospheric nitrogen to generate all their nitrogenous components.
Heterotrophs cannot use atmospheric carbon dioxide and must obtain carbon from their
environment in the form of relatively complex organic molecules such as glucose.
The major principles of metabolism are:
1. Fuels are degraded and large molecules are constructed step by step in a series of linked
reactions called metabolic pathways.
2. An energy currency common to all life forms, adenosine triphosphate (ATP), links energy-
releasing pathways with energy-requiring pathways.
Reducing powers are also essential components of the metabolic pathway: they include NADH
+H+, FADH2 and to a less extent NADPH +H+
3. The oxidation of carbon fuels powers the formation of ATP.
4. Although there are many metabolic pathways, a limited number of types of reactions and
particular intermediates are common to many pathways.
5. Metabolic pathways are highly regulated.

6. Thermodynamically unfavourable reactions are usually coupled to make them favourable
GLUCOSE METABOLISM
Overview of glucose metabolism
Glucose is a key metabolite in human metabolism, and we will discuss several pathways that are
concerned with the utilization, storage, and regeneration of glucose. The first step in the
degradation of glucose is glycolysis, which breaks down glucose to pyruvate. The main purpose
of glycolysis is the generation of energy (ATP); a modest amount is generated directly, and a lot
more indirectly through the subsequent oxidation of substrate carbon in the citric acid cycle and
of hydrogen in the respiratory chain. The need for ATP is universal, which means that the
glycolytic pathway is active in every cell of our body.
The hexose monophosphate shunt also can break down glucose completely, but the main product
is NADPH rather than ATP. NADPH is universally needed as a reducing agent, and accordingly
this pathway is ubiquitous, too.
Glycogen is a polymeric storage form of glucose, not unlike starch, which is found in plants.
This pathway is quantitatively most important in the liver and in striated muscle, although some
glycogen is found in other tissues also. Glycogen molecules remain inside the same cells that
synthesized them; therefore, breakdown of glycogen to glucose again occurs predominantly in
liver and muscle. Glycogen degradation is activated when the current external supply of glucose
is low, as it is between meals. In the liver, the glucose generated from glycogen is released into
the general circulation. Glycogen in skeletal muscle can contribute to the supply of blood
glucose, but it is mostly utilized by muscle itself for regenerating ATP during physical exercise.
Gluconeogenesis turns pyruvate into glucose; it thus is essentially the reversal of glycolysis. This
pathway, too, is activated in times of low external glucose supply. Its most important substrates
are amino acids, which are obtained either from a protein rich diet—for example, when we feast
on meat exclusively—or, during starvation, from breakdown of cellular protein, mainly in
skeletal muscle. Gluconeogenesis occurs in the liver and in the kidneys.
The place of glycolysis in glucose degradation
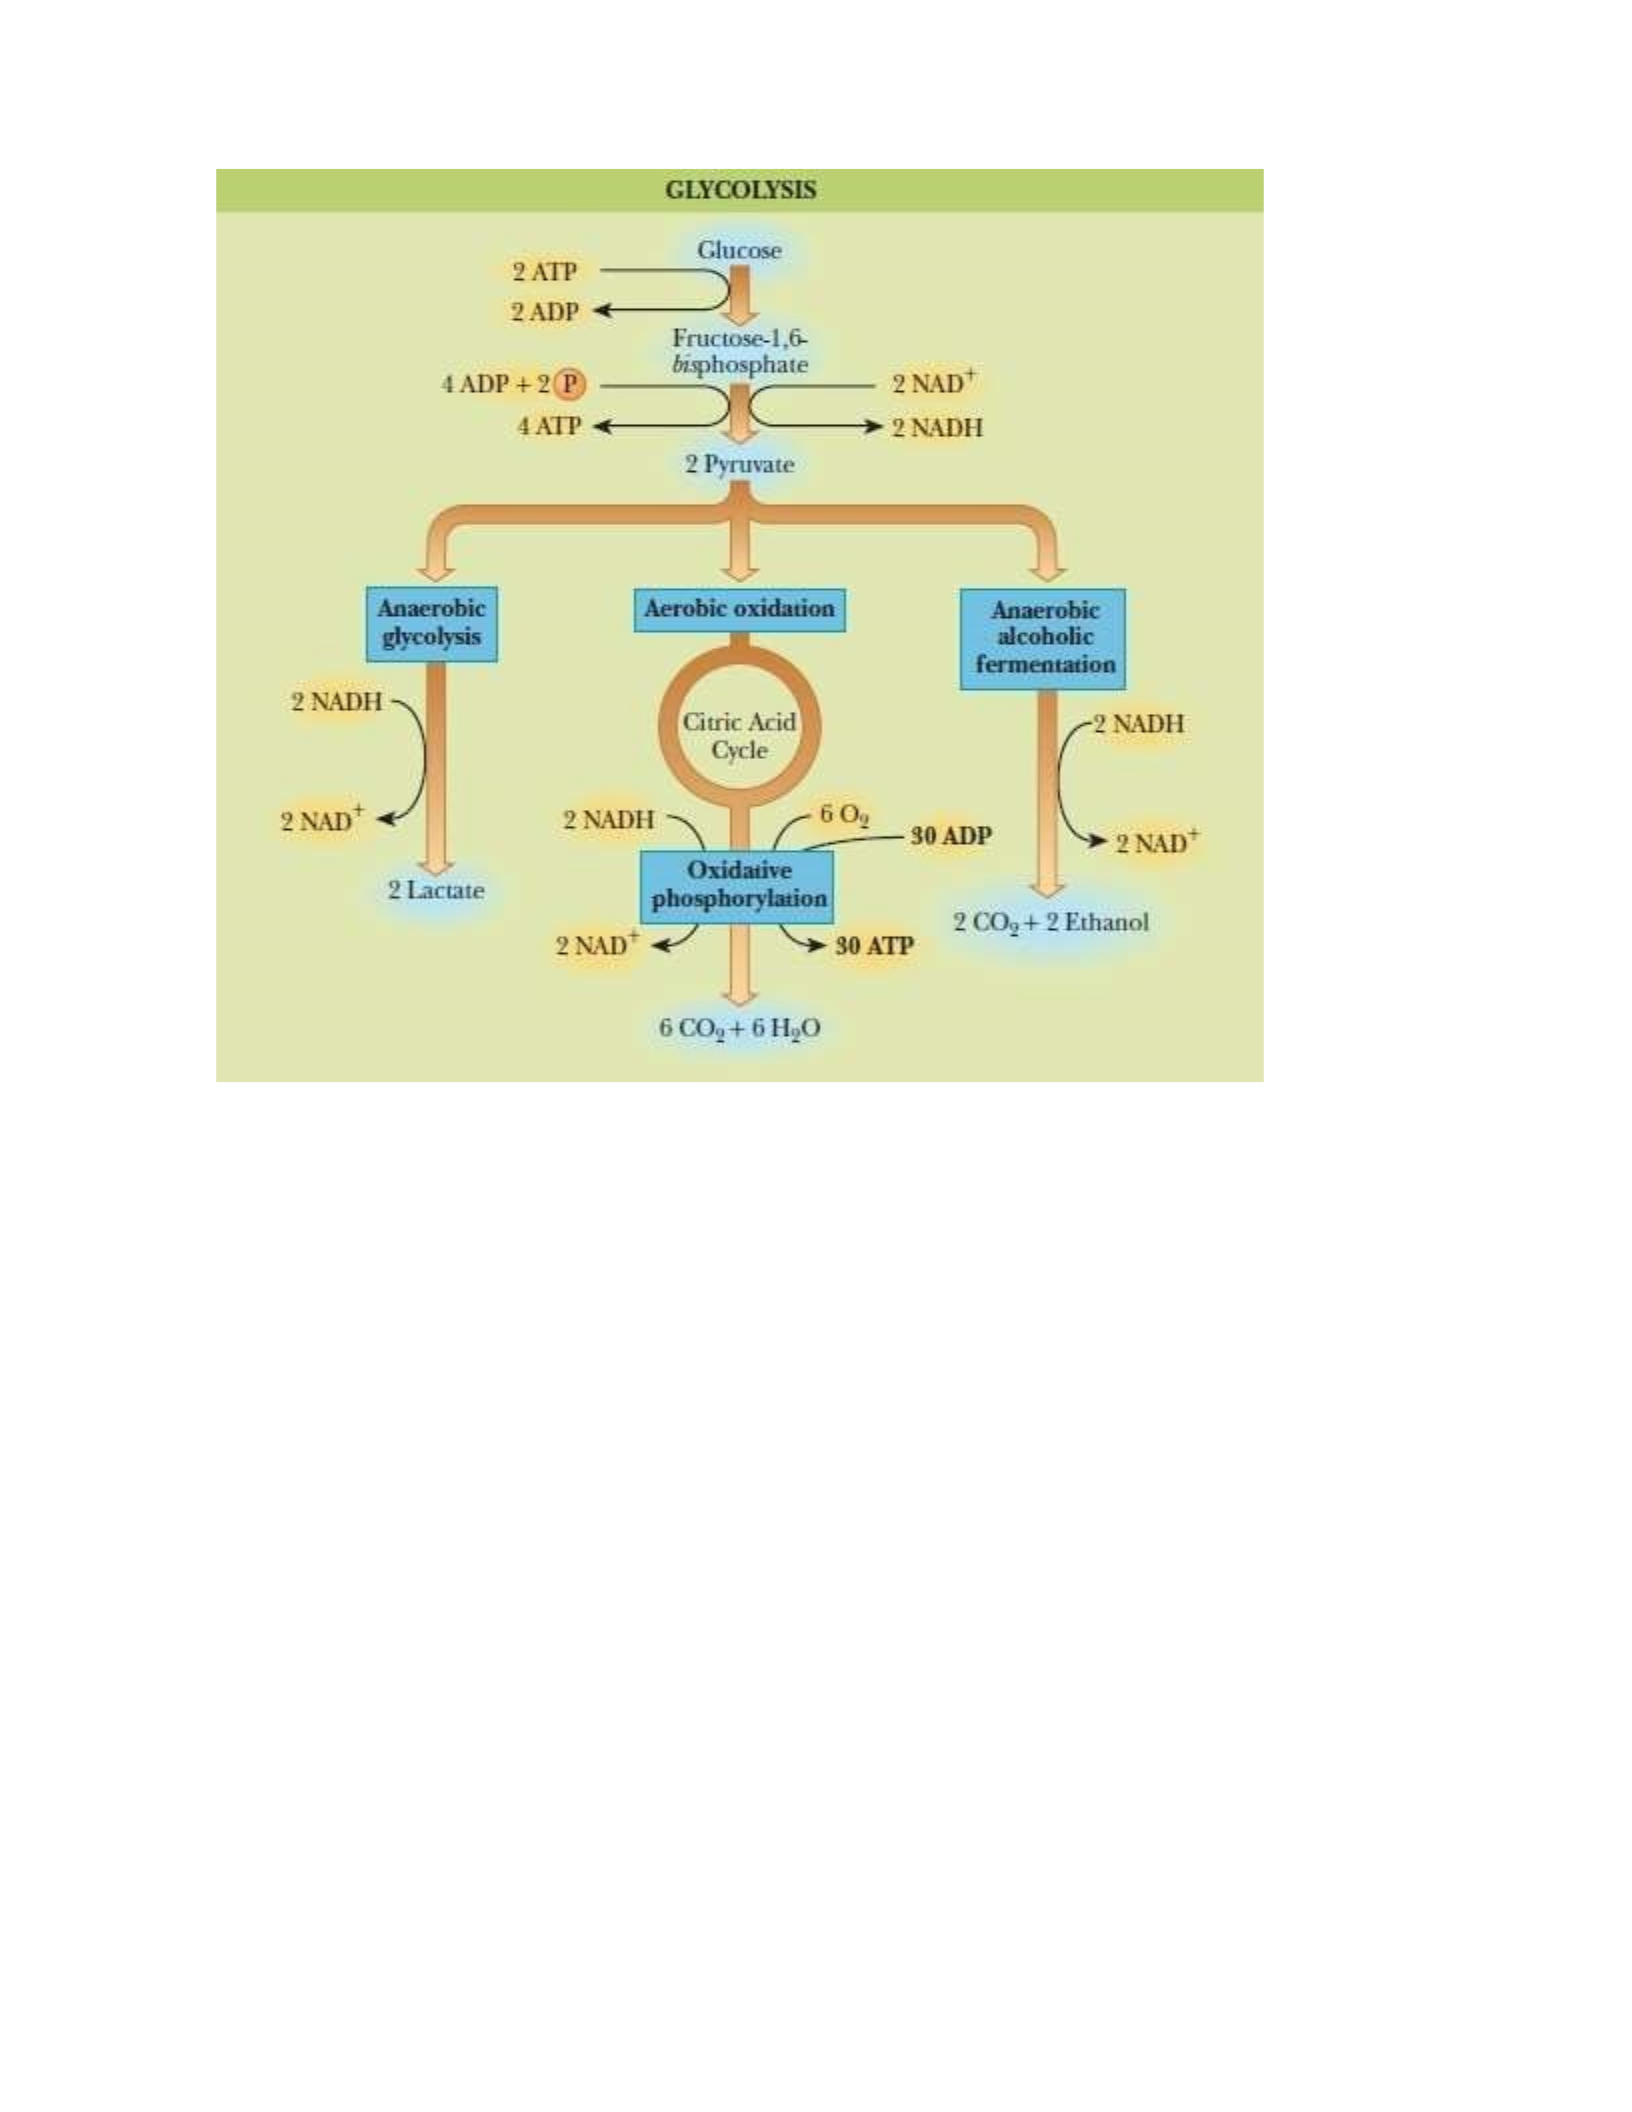
As noted above, glycolysis is only the first stage of glucose degradation. Under aerobic
conditions, most of the pyruvate formed in glycolysis undergoes complete oxidative degradation
to CO2 and H2O. Pyruvate destined for complete degradation is transported to the mitochondria,
where it is decarboxylated to acetyl-CoA by pyruvate dehydrogenase (PDH). Acetyl-CoA is
completely degraded in the citric acid cycle (or tricarboxylic acid cycle, TCA cycle for short).
The “H2” that is produced here is not gaseous but bound to co-substrates, as NADH + H+ and
FADH2, respectively. It is oxidized in the respiratory chain, which yields most of the ATP that is
produced in the overall process of glucose degradation. If glucose is available in excess of
immediate needs and glycogen is already stocked up to capacity, it will still be broken down by
glycolysis and pyruvate dehydrogenase to acetyl-CoA. However, acetyl-CoA will then be used
for fatty acid synthesis; the fatty acids are converted to triacylglycerol. Fatty acid synthesis
occurs in the cytosol of cells in the liver and fat tissue.
Reactions in glycolysis
In glycolysis, one molecule of glucose (a six-carbon compound) is converted to fructose-1,6-
bisphosphate (also a six-carbon compound), which eventually gives rise to two molecules of
pyruvate (a three-carbon compound).
The glycolytic pathway (also called the Embden–Meyerhoff pathway) involves many steps,
including the reactions in which metabolites of glucose are oxidized.
In the entire glycolysis process 2ATP molecules are utilised and 4ATP molecules are produced
giving an ultimate gain in 2ATP molecules.
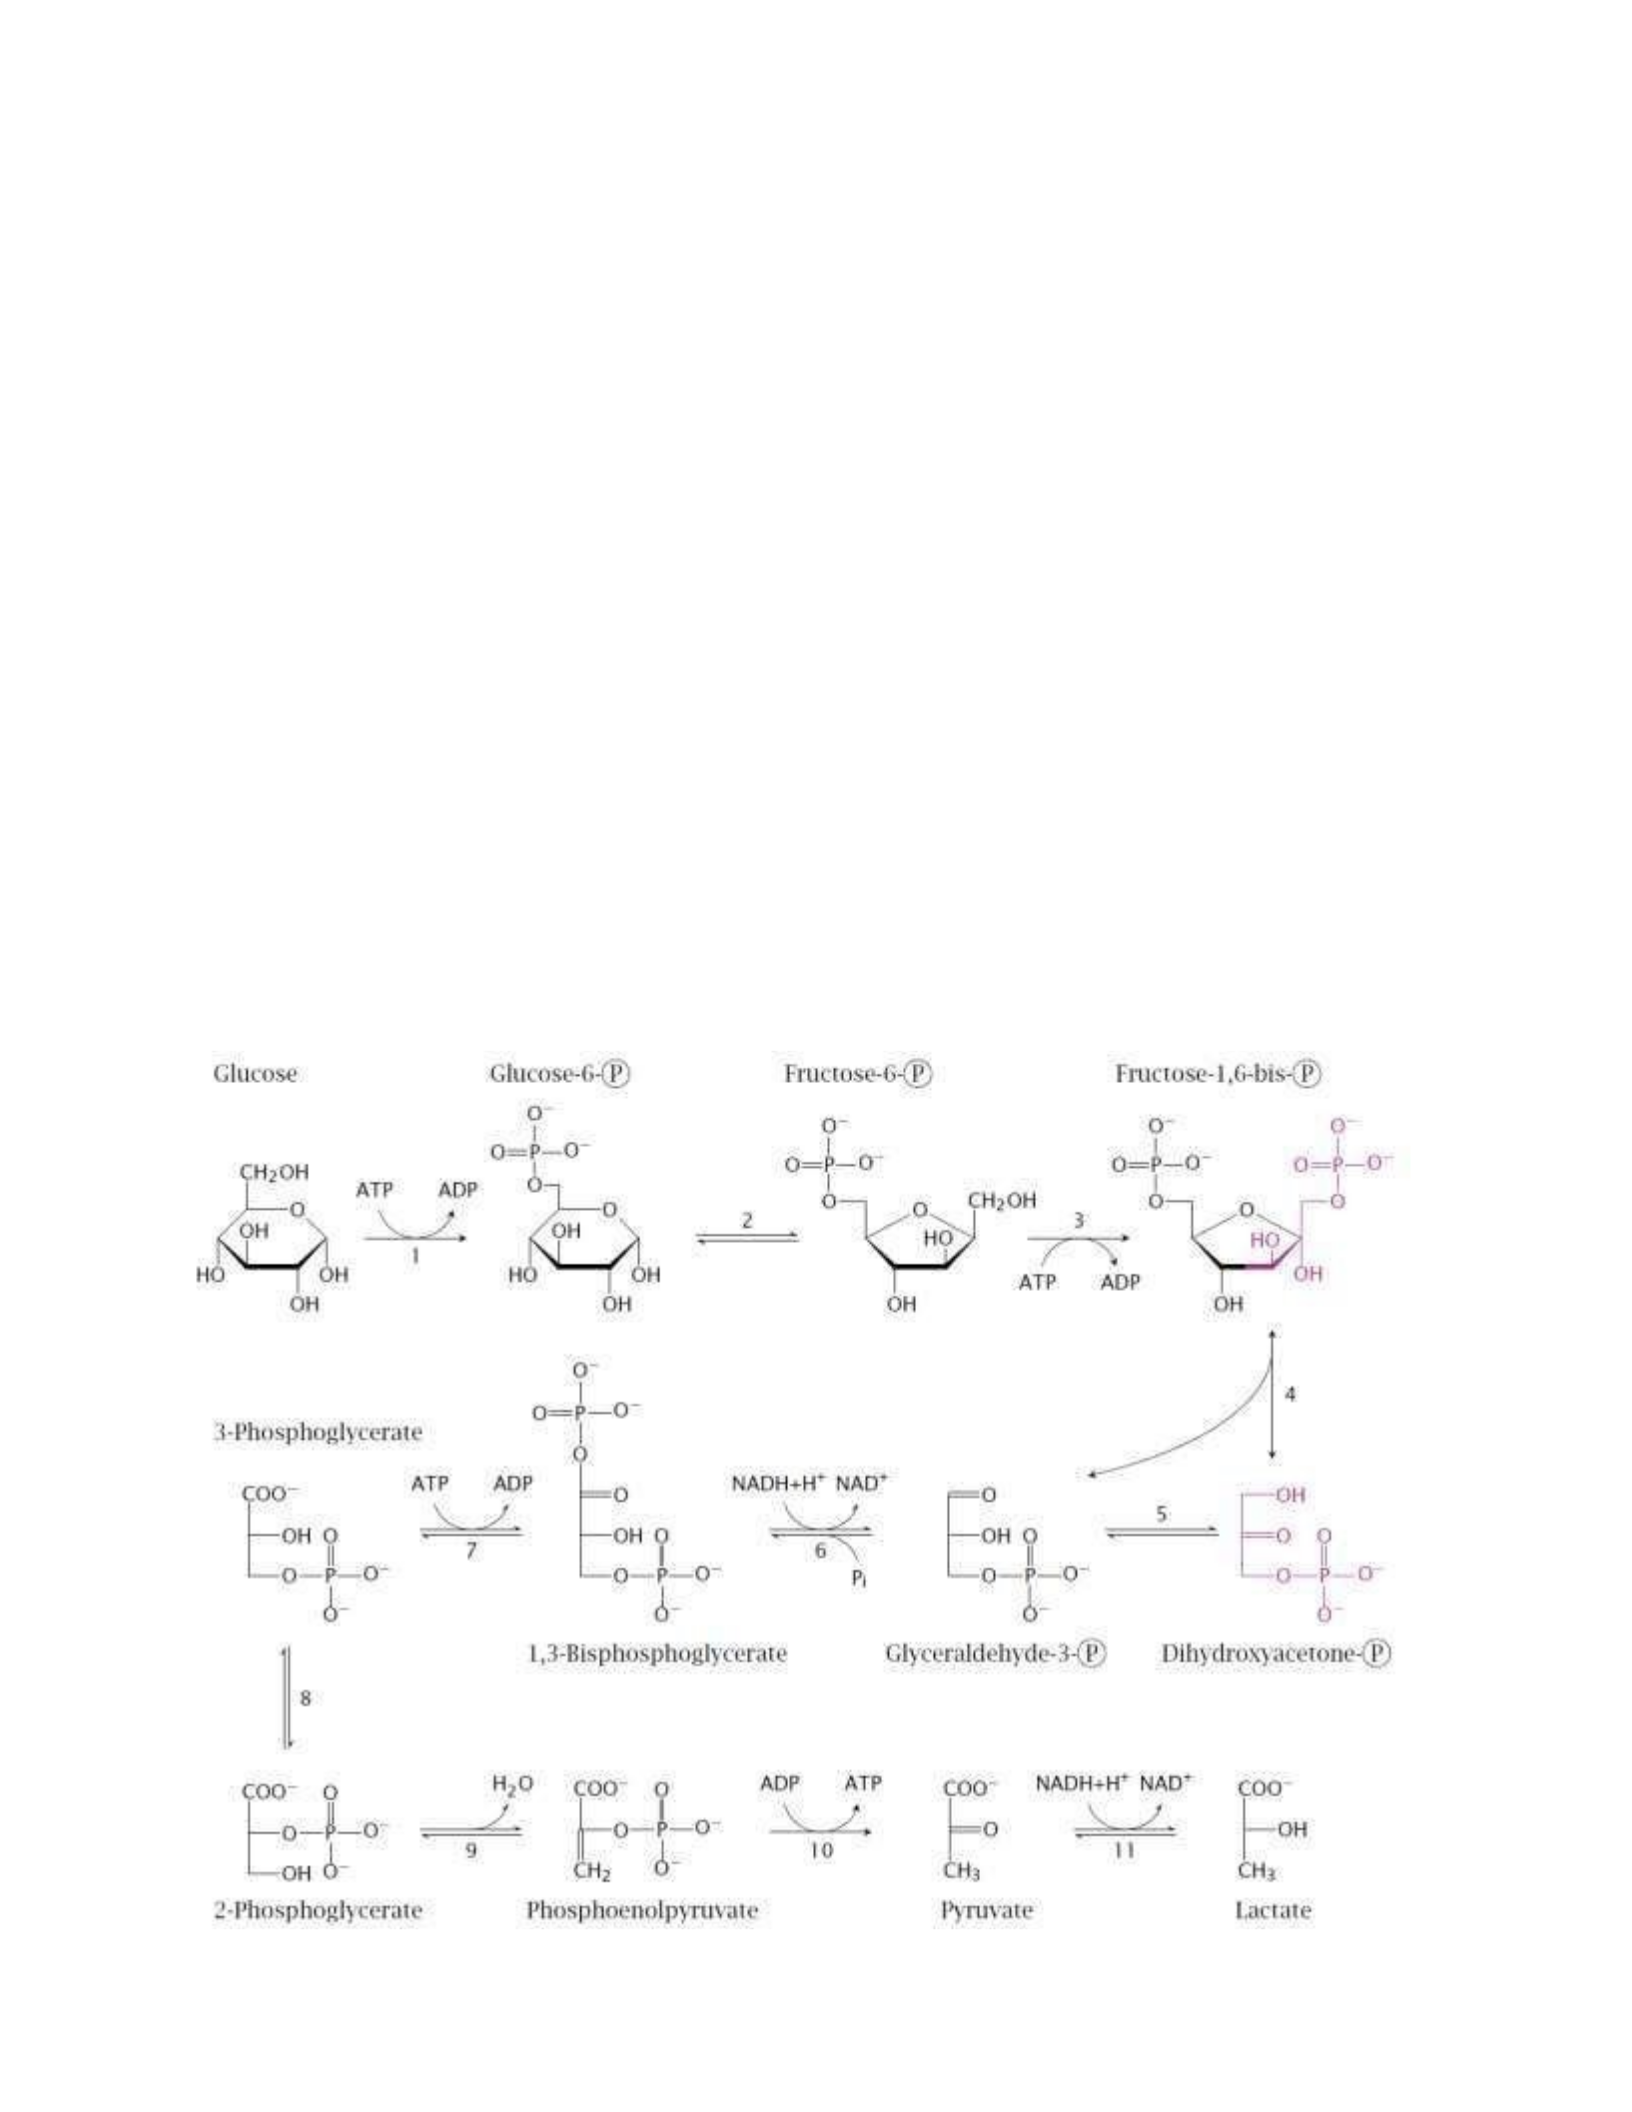
Notes: Glycolysis involves 10 enzymatic reactions, as follows:
1. The phosphorylation of glucose at position 6 by hexokinase,
2. The isomerization of glucose-6-phosphate to fructose-6-phosphate by phosphohexose
isomerase,
3. The phosphorylation of fructose-6-phosphate to the 1,6-bisphosphate by phosphofructokinase,
4. the cleavage of fructose-1,6-bisphosphate by aldolase. This yields two different products,
dihydroxyacetone phosphate and glyceraldehyde-3-phosphate,
5. the isomerization of dihydroxyacetone phosphate to a second molecule of glyceraldehyde
phosphate by triose phosphate isomerase,
6. the dehydrogenation and concomitant phosphorylation of glyceraldehyde-3-phosphate to 1,3-
bis-phosphoglycerate by glyceraldehyde-3-phosphate dehydrogenase,
7. the transfer of the 1-phosphate group from 1,3-bis-phosphoglycerate to ADP by
phosphoglycerate kinase, which yields ATP and 3-phosphoglycerate,
8. the isomerization of 3-phosphoglycerate to 2-phosphoglycerate by phosphoglycerate mutase,
9. the dehydration of 2-phosphoglycerate to phosphoenolpyruvate by enolase, and finally
10. the transfer of the phosphate group from phosphoenolpyruvate to ADP by pyruvate
kinase, to yield a second molecule of ATP.
Most of the pyruvate produce in step 10 undergoes oxidative degradation in the mitochondria.
The 11th reaction, catalyzed by lactate dehydrogenase, mostly occurs under anaerobic
conditions, or in those cells that have no mitochondria and therefore lack the ability to
oxidatively degrade pyruvate altogether. The latter applies to red blood cells and thrombocytes.
Most, but not all reactions in glycolysis are reversible; this is indicated in the slide by double and
single arrows, respectively. As such, the pathway as a whole is also irreversible.
Glycolysis under aerobic and anaerobic conditions
The complete oxidative (aerobic) degradation of each glucose molecule yields approximately 30
molecules of ATP. How much of this accrues in glycolysis?
The initial phosphorylation reactions (steps 1 and 3 of glycolysis) expend two molecules of ATP.
One molecule of ATP is obtained in steps 7 and 10 each. Since all of the steps from 6 to 10 occur
twice per molecule of glucose, the net balance is a gain of two moles of ATP per mole of glucose
— a very modest contribution to the final tally. Still, glycolysis is a viable source of ATP, and it
is the major one that operates in our tissues under anaerobic conditions, that is, while oxygen is
in short supply. This concerns mostly skeletal muscle during maximal exercise, such as a 100
meter dash.
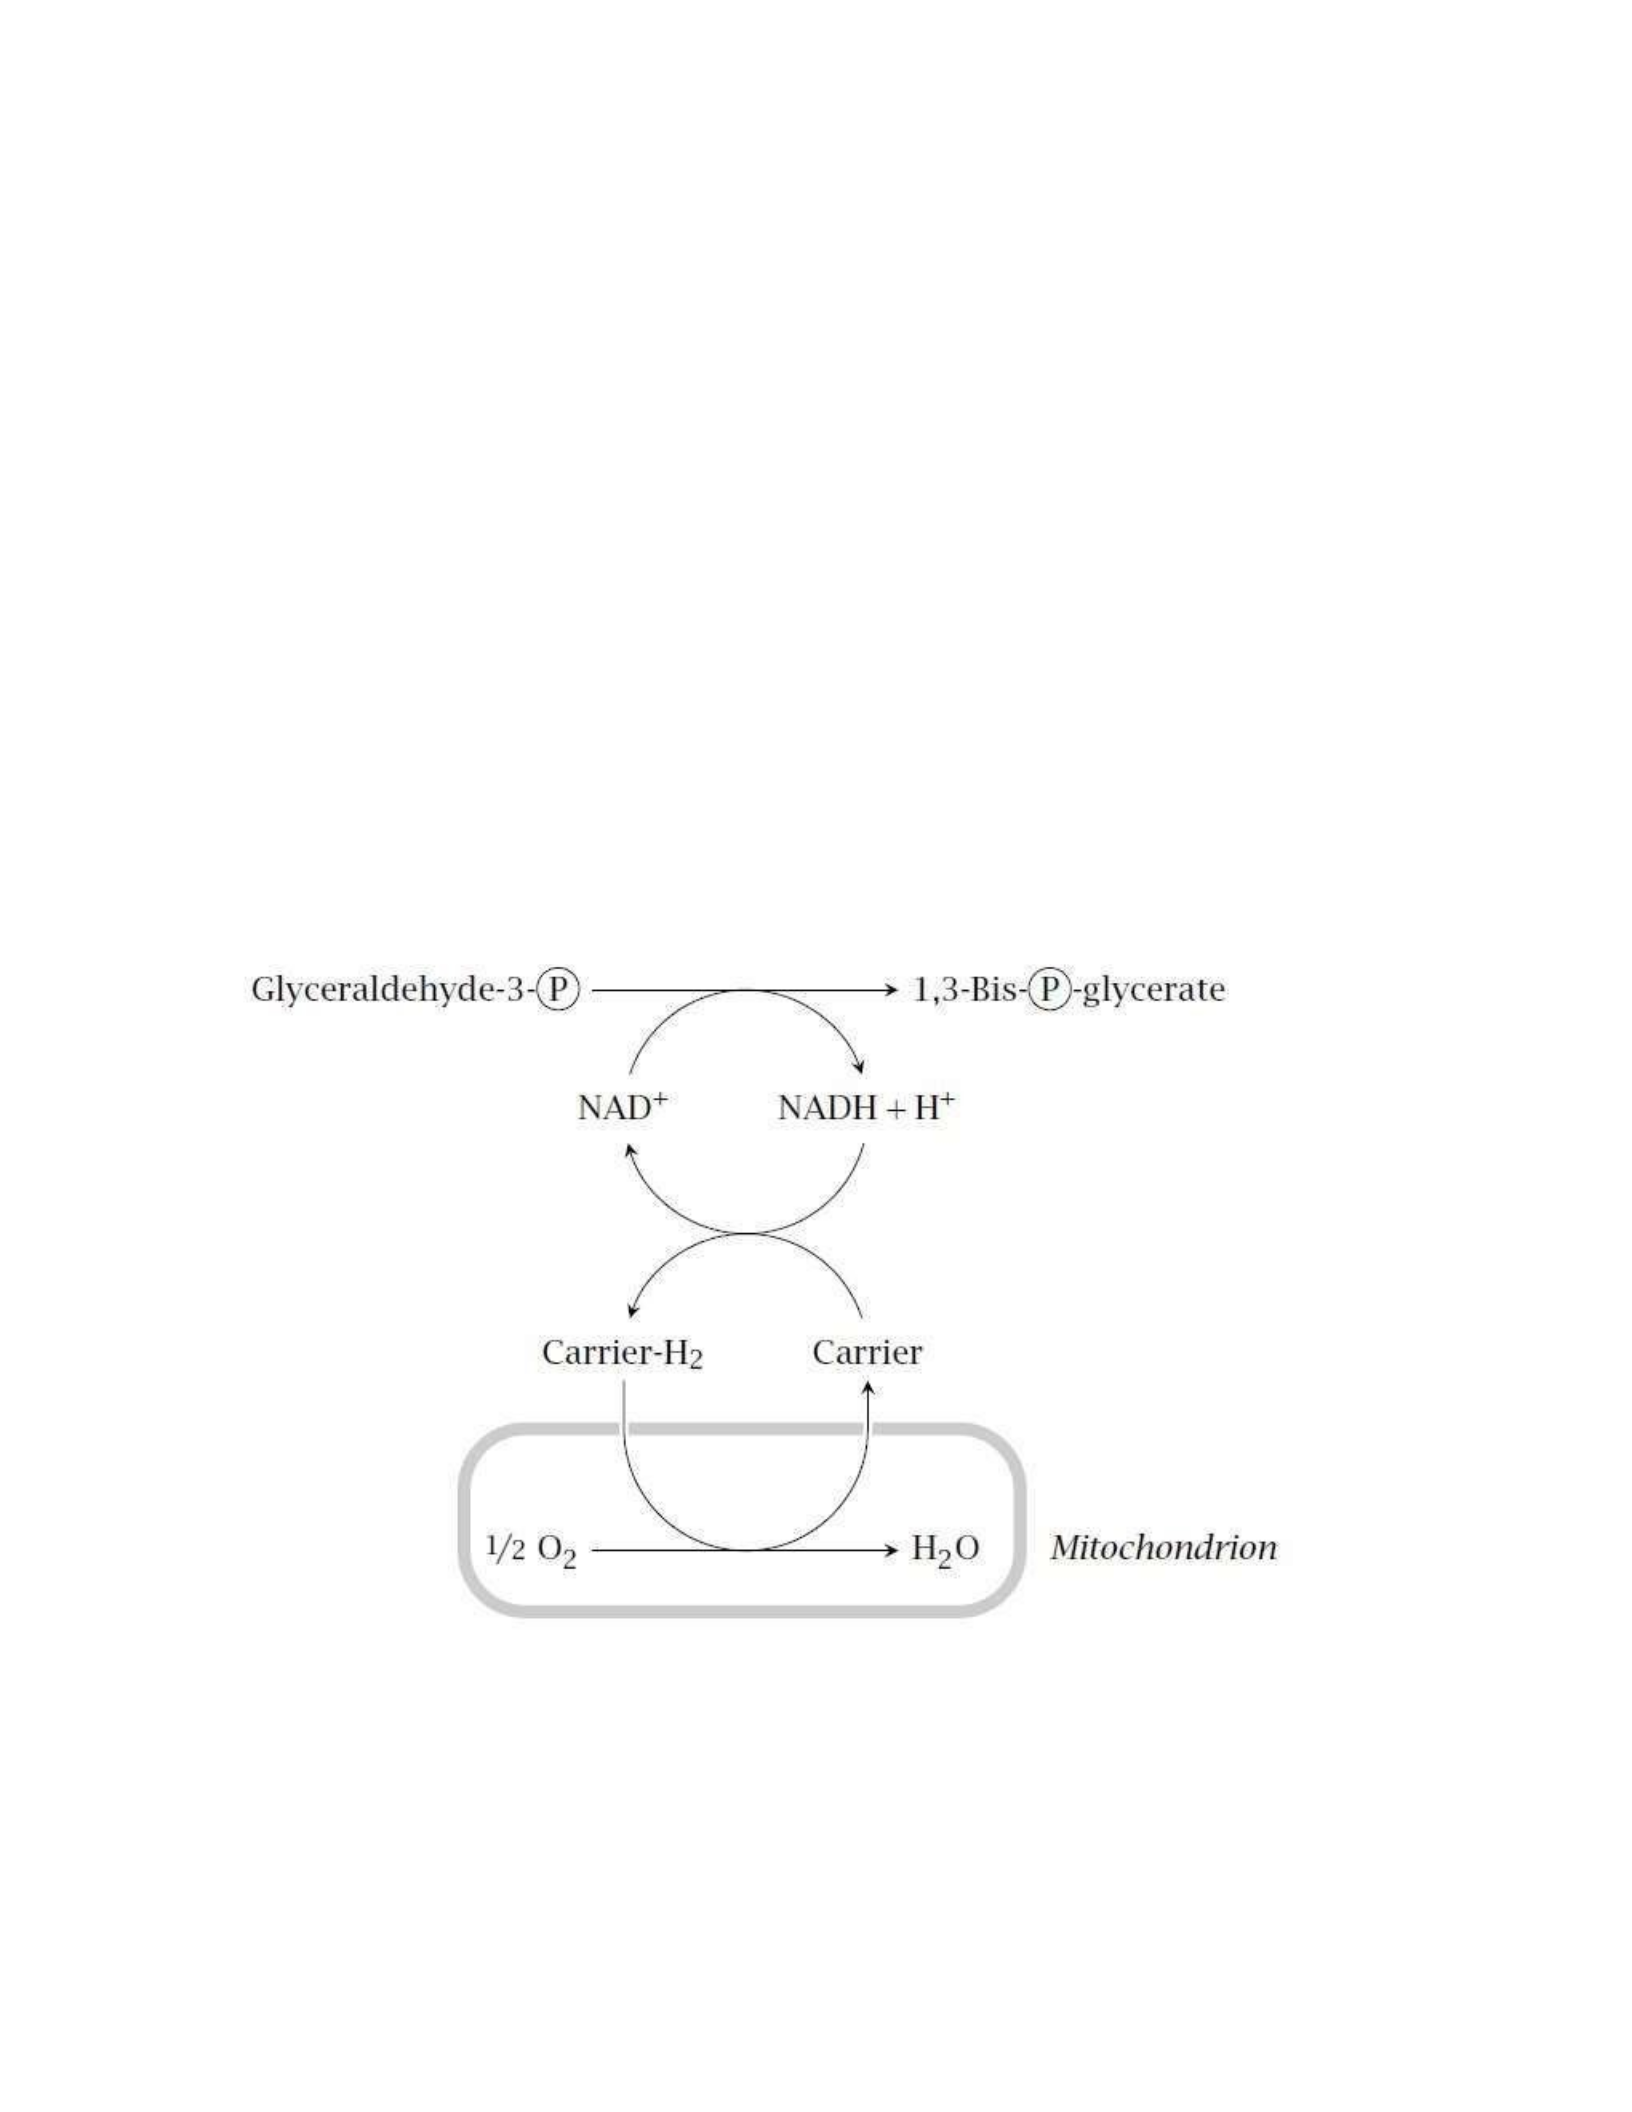
Regeneration of cytosolic NAD+ under aerobic conditions
The glyceraldehyde-3-phosphate dehydrogenase reaction (step 6 in glycolysis) reduces one
equivalent of NAD+ to NADH. Under aerobic conditions, the hydrogen is transferred to various
carriers that deliver it to the respiratory chain in the mitochondria, and ultimately to oxygen.
Under anaerobic conditions, this is impossible; therefore, other means for hydrogen disposal are
required.
Under anaerobic conditions,
There are two fates for pyruvate in anaerobic metabolism (in the absence of oxygen). In
organisms capable of alcoholic fermentation, pyruvate loses carbon dioxide, this time
producing acetaldehyde, which, in turn, is reduced to produce ethanol. The more common
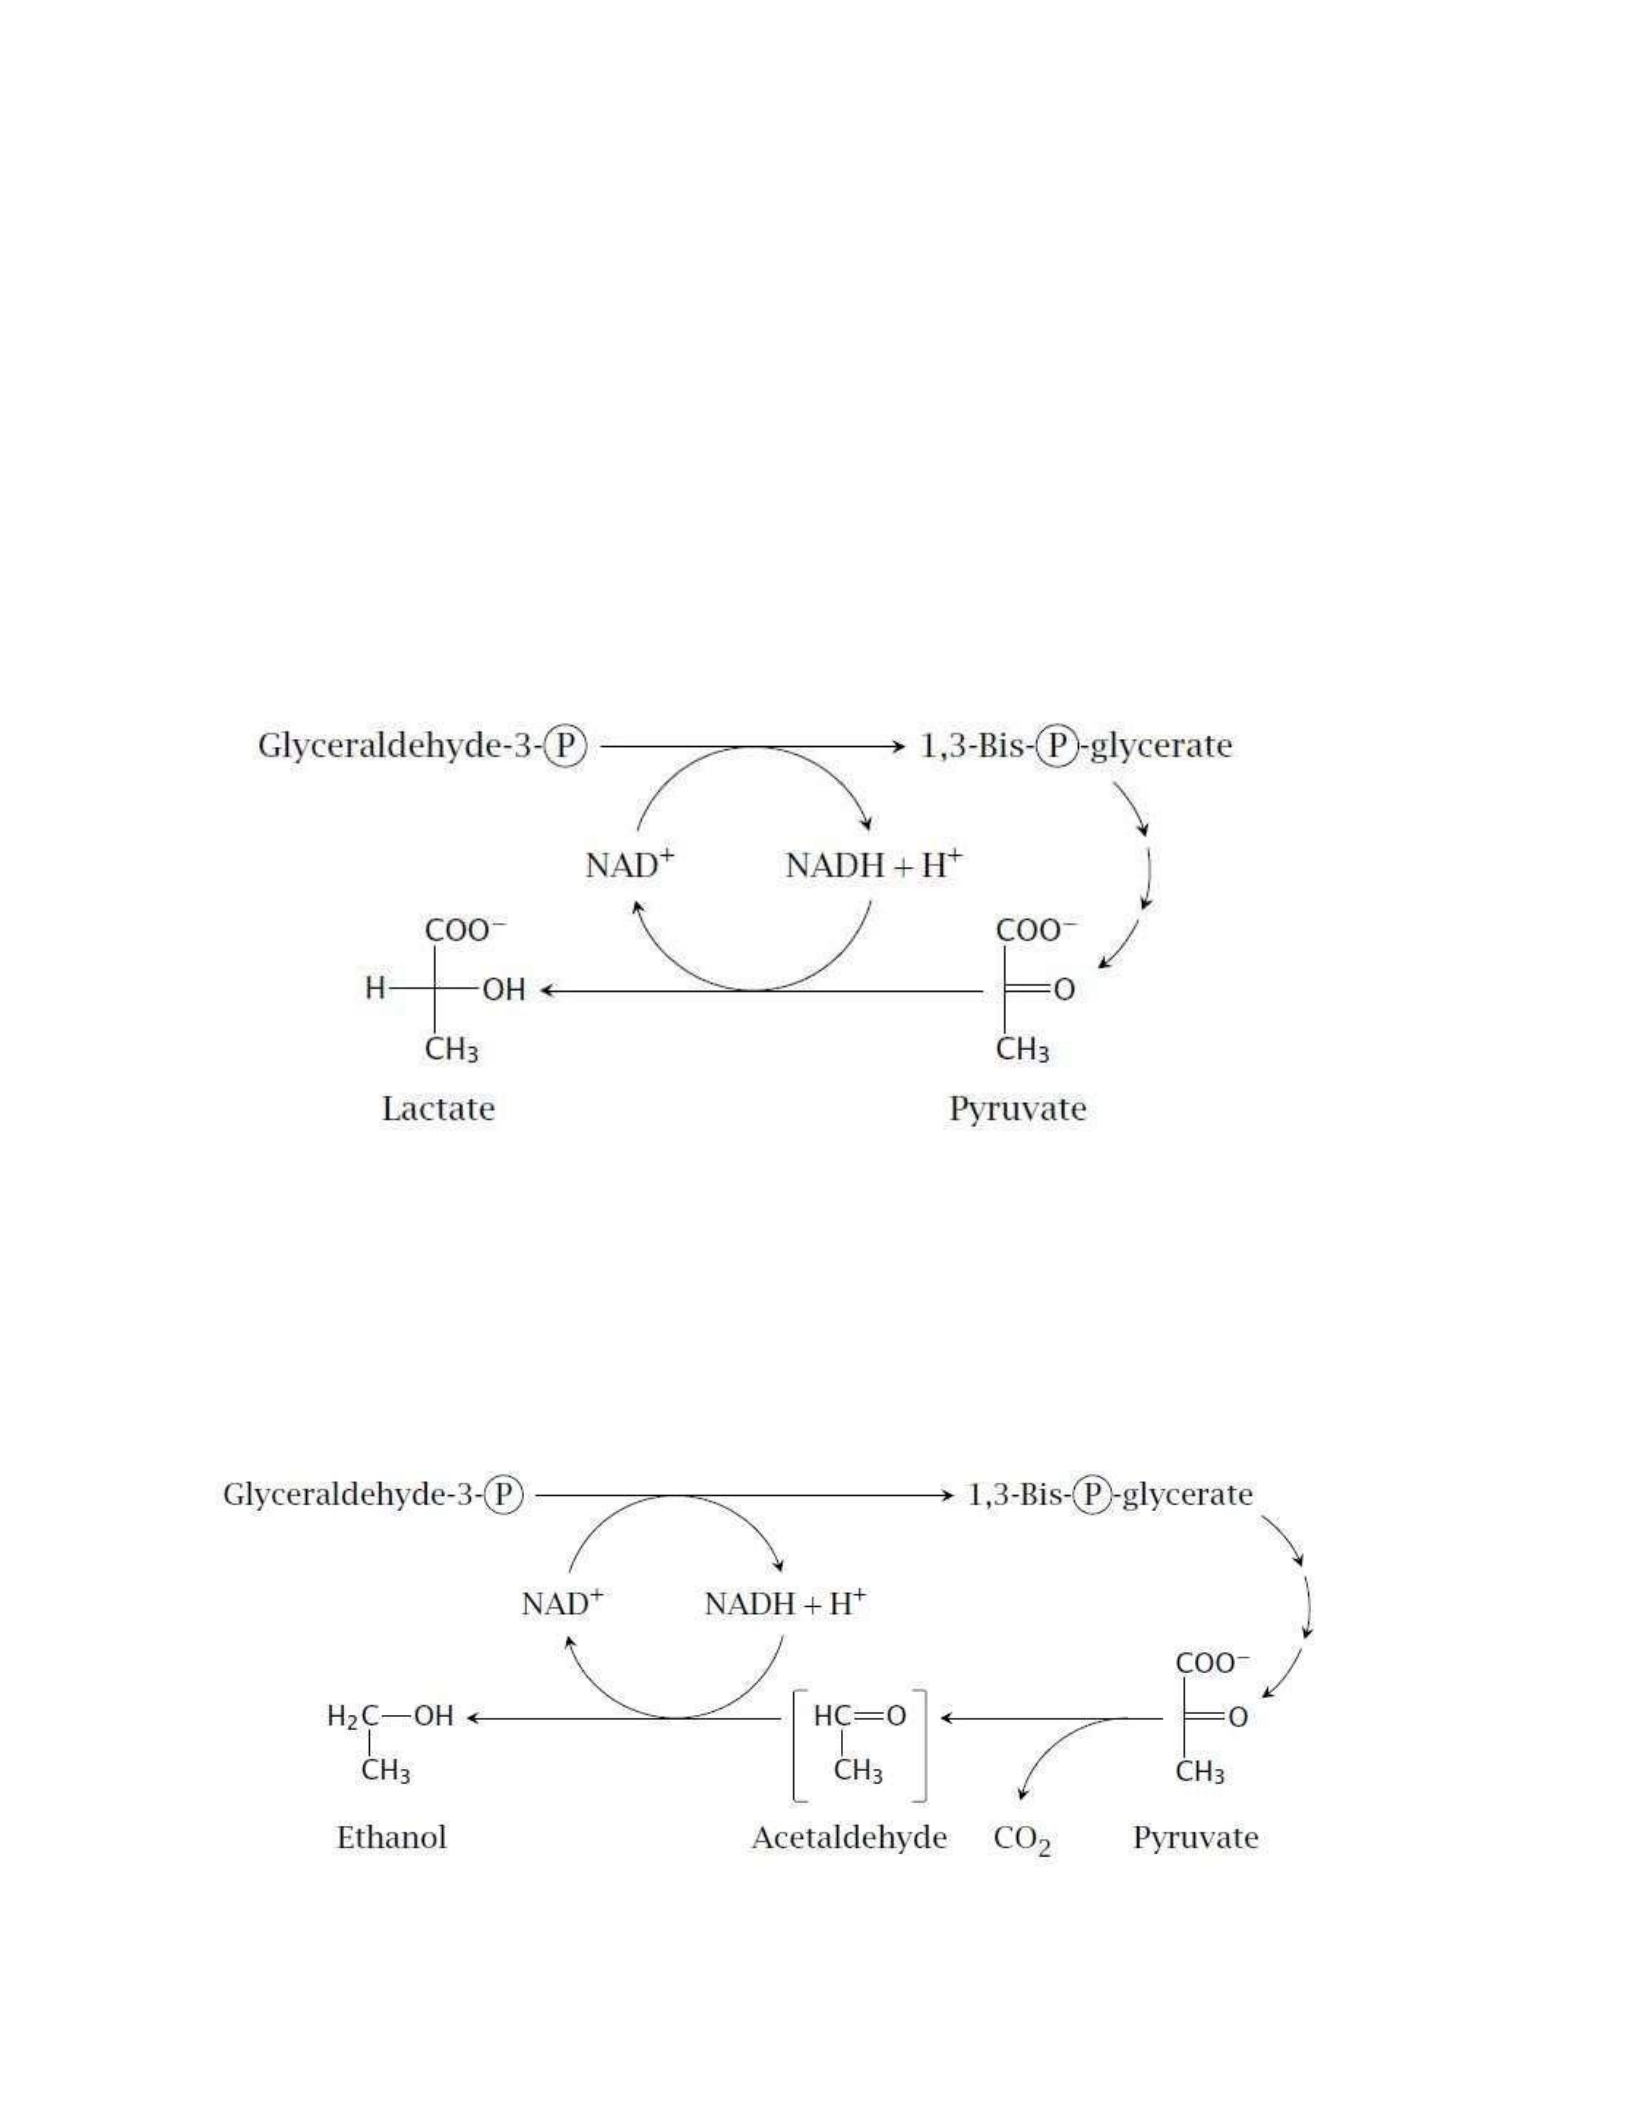
fate of pyruvate in anaerobic metabolism is reduction to lactate, called anaerobic
glycolysis to distinguish it from conversion of glucose to pyruvate, which is simply called
glycolysis. Anaerobic metabolism is the only energy source in mammalian red blood cells,
as well as in several species of bacteria, such as Lactobacillus in sour milk and Clostridium
botulinum in tainted canned foods. In all these reactions, the conversion of glucose to
product is an oxidation reaction, requiring an accompanying reduction reaction in which
NAD+ is converted to NADH, a point to which we shall return when we discuss the
pathway in detail.
1. NAD+ is regenerated by lactate dehydrogenase
In human metabolism, pyruvate serves as the makeshift hydrogen acceptor; it is reduced to
lactate by lactate dehydrogenase (step 11 in glycolysis). The lactate is released into the
bloodstream, where it accumulates; it is removed and recycled after restoration of aerobic
conditions. The muscle pain caused by lactate accumulation forces us to discontinue anaerobic
exercise after a short while.
2. Ethanolic fermentation in yeast serves a dual purpose
Notes: Anaerobic glycolysis also occurs in many microbes, which face the same problem of
NADH disposal. Without the option of reverting to oxidative metabolism within a short time
span, they must also deal with the accumulation of acid. The yeast Saccharomyces cerevisiae

solves this problem through ethanolic fermentation: The acid is converted to a neutral and
considerably less toxic compound (ethanol) via decarboxylation. The CO2 developed in this
reaction makes bread dough rise up, whereas the ethanol does the same to provincial tax revenue.
Some cells in the human body, most notably the erythrocytes (red blood cells), rely entirely on
anaerobic glycolysis for ATP production even under aerobic conditions, since they lack
mitochondria and therefore the ability to oxidize pyruvate.
DIETARY SUGARS OTHER THAN GLUCOSE (FEEDER PATHWAYS)
Many carbohydrates besides glucose meet their catabolic fate in glycolysis, after being
transformed into one of the glycolytic intermediates. The most significant are the storage
polysaccharides glycogen and starch, either within cells (endogenous) or obtained in the
diet; the disaccharides maltose, lactose, trehalose, and sucrose; and the monosaccharides
fructose, mannose, and galactose
Dietary Polysaccharides and Disaccharides Undergo Hydrolysis to Monosaccharides
For most humans, starch is the major source of carbohydrates in the diet (Fig. 14–10).
Digestion begins in the mouth, where salivary α-amylase hydrolyzes the Internal (α1n4)
glycosidic linkages of starch, producing short polysaccharide fragments or
oligosaccharides. (Note that in this hydrolysis reaction, water, not Pi, is the attacking
species.) In the stomach, salivary _-amylase is inactivated by the low pH, but a second
form of α_-amylase, secreted by the pancreas into the small intestine, continues the
breakdown process. Pancreatic _amylase yields mainly maltose and maltotriose (the di-
and trisaccharides of glucose) and oligosaccharides called limit dextrins, fragments of
amylopectin containing (_1n6) branch points. Maltose and dextrins are degraded to
glucose by enzymes of the intestinal brush border (the fingerlike microvilli of intestinal
epithelial cells, which greatly increase the area of the intestinal surface). Dietary glycogen
has essentially the same structure as starch, and its digestion proceeds by the same
pathway.
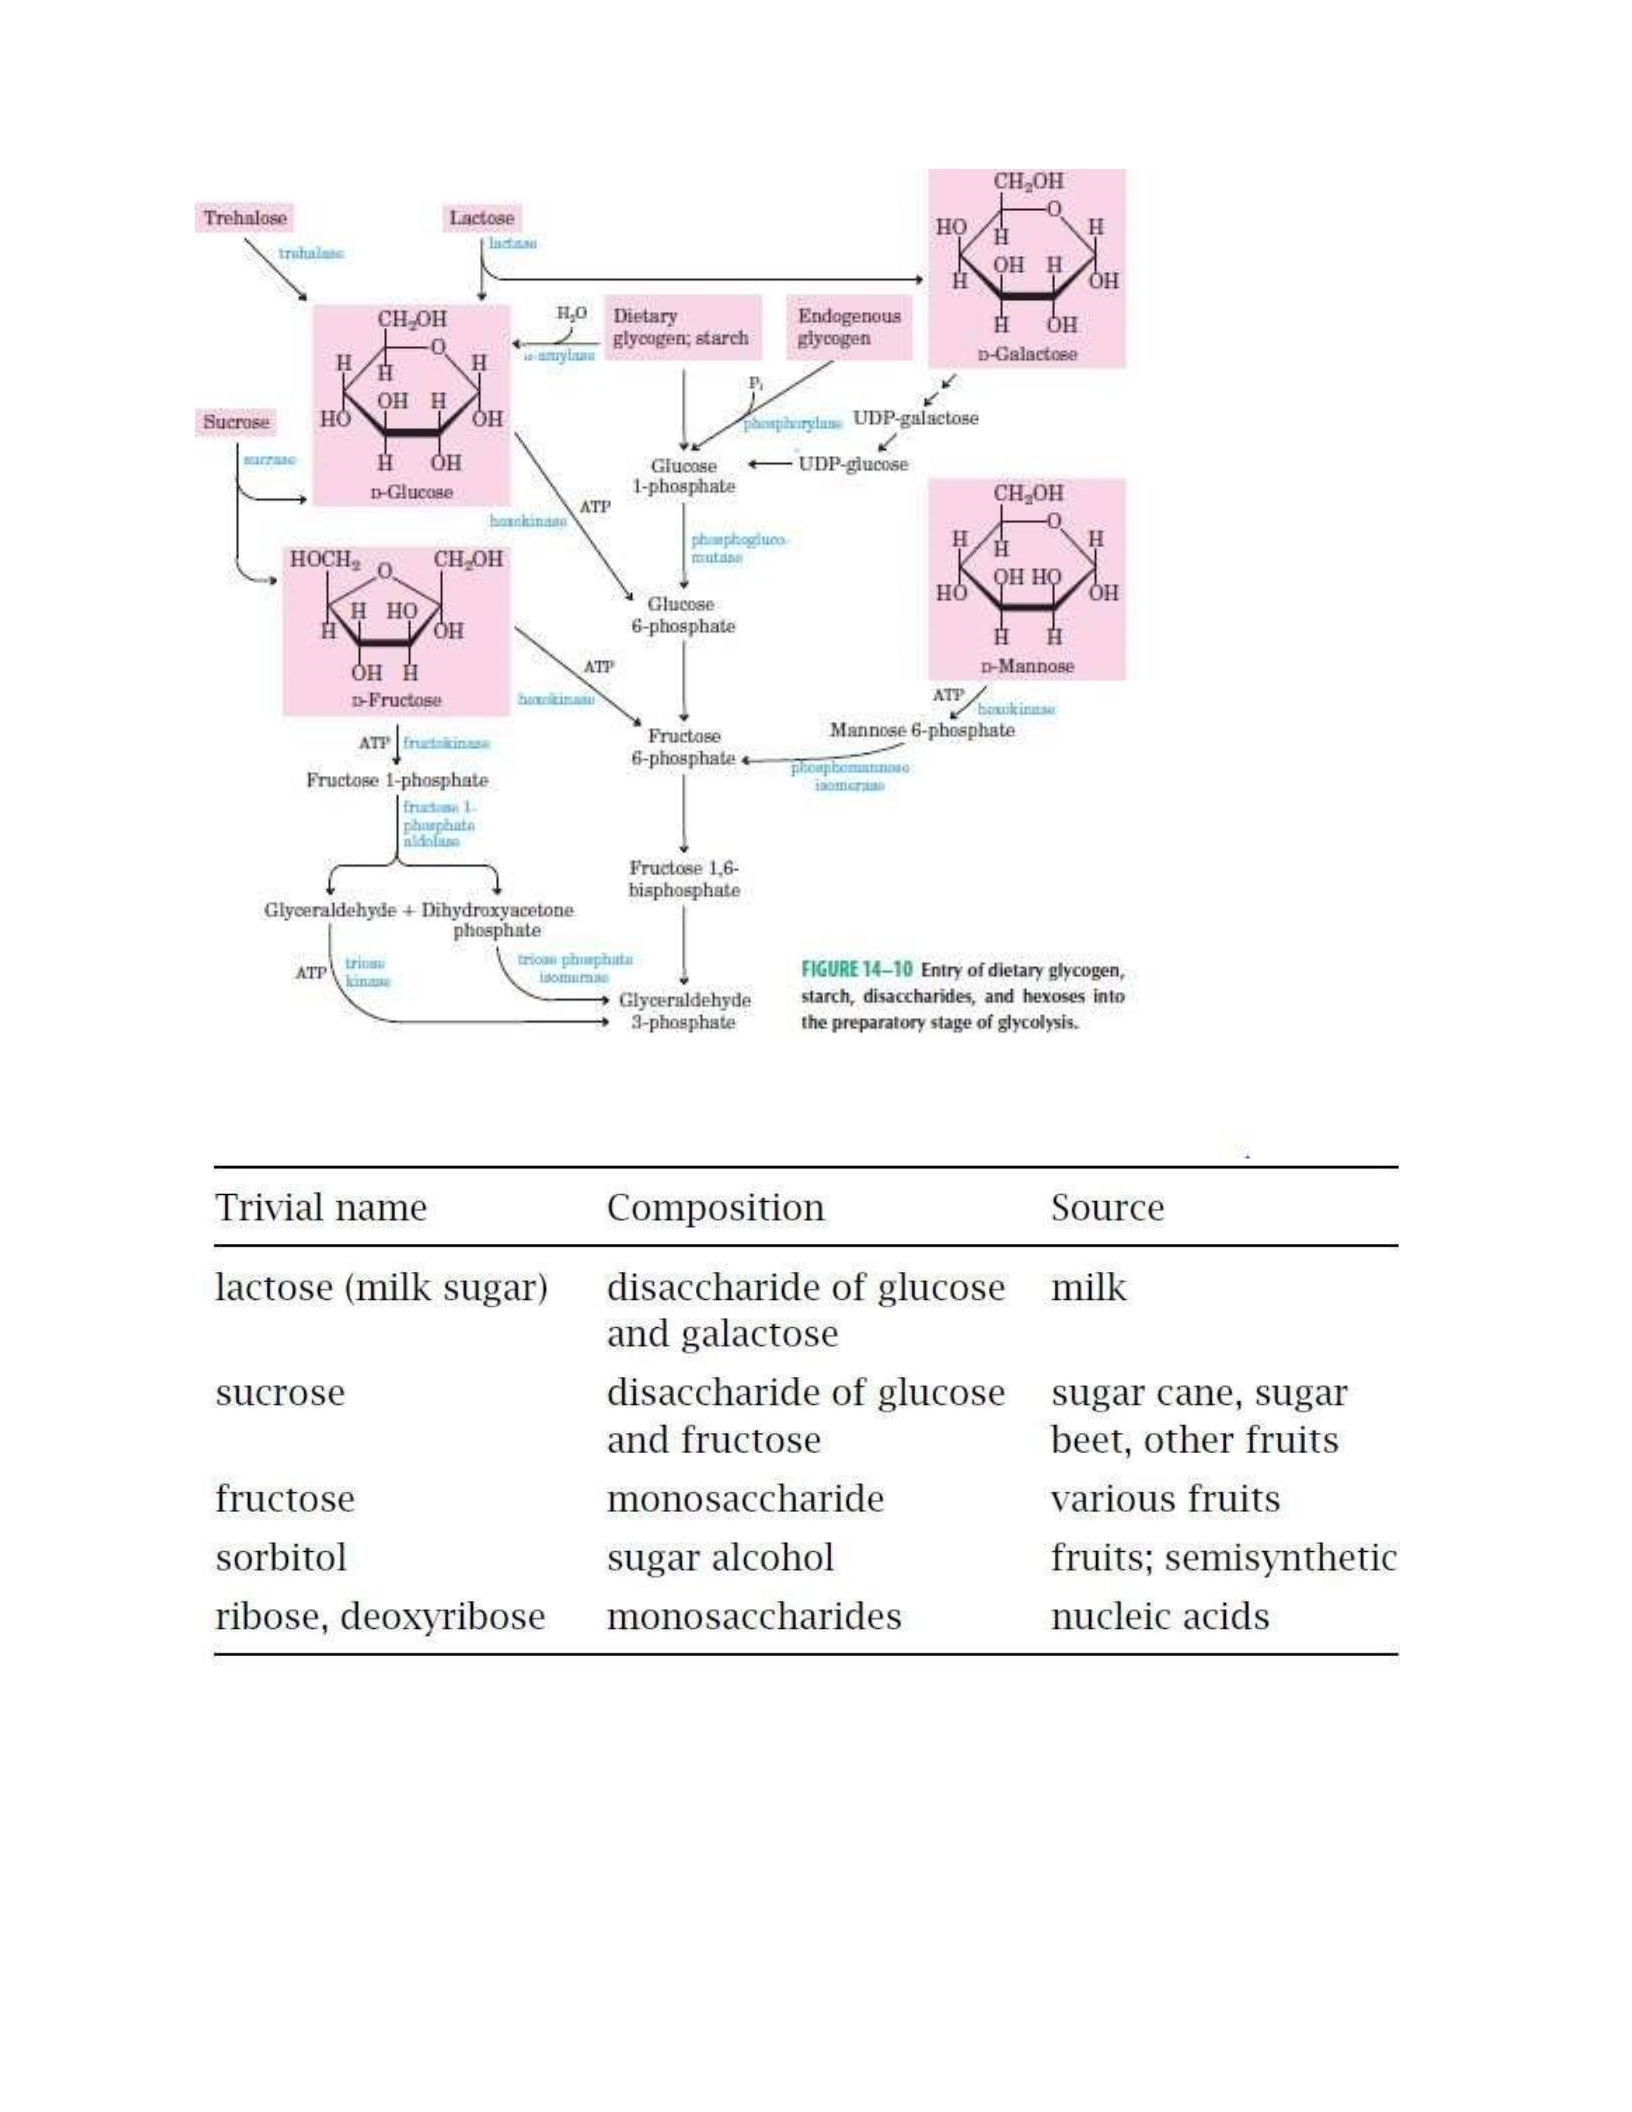
Notes: Starch is the most abundant carbohydrate in our diet, which makes glucose the most
important dietary monosaccharide. However, our diet contains several other quantitatively
significant sugars. The main motif in the metabolism of these sugars is economy: instead of
completely separate degradative pathways, there are short adapter pathways that merge into the
main pathway of carbohydrate degradation, namely glycolysis.
Lactose and sucrose are disaccharides. Degradation of both begins with hydrolytic cleavage,
which releases glucose and galactose or fructose, respectively. We already know how glucose is
degraded, so we here only need to concern ourselves with the remaining monosaccharides.
transporter, and fructose by the GLUT5 transporter, which is named after glucose but actually
transports fructose more effectively than glucose.
Lactose and galactose
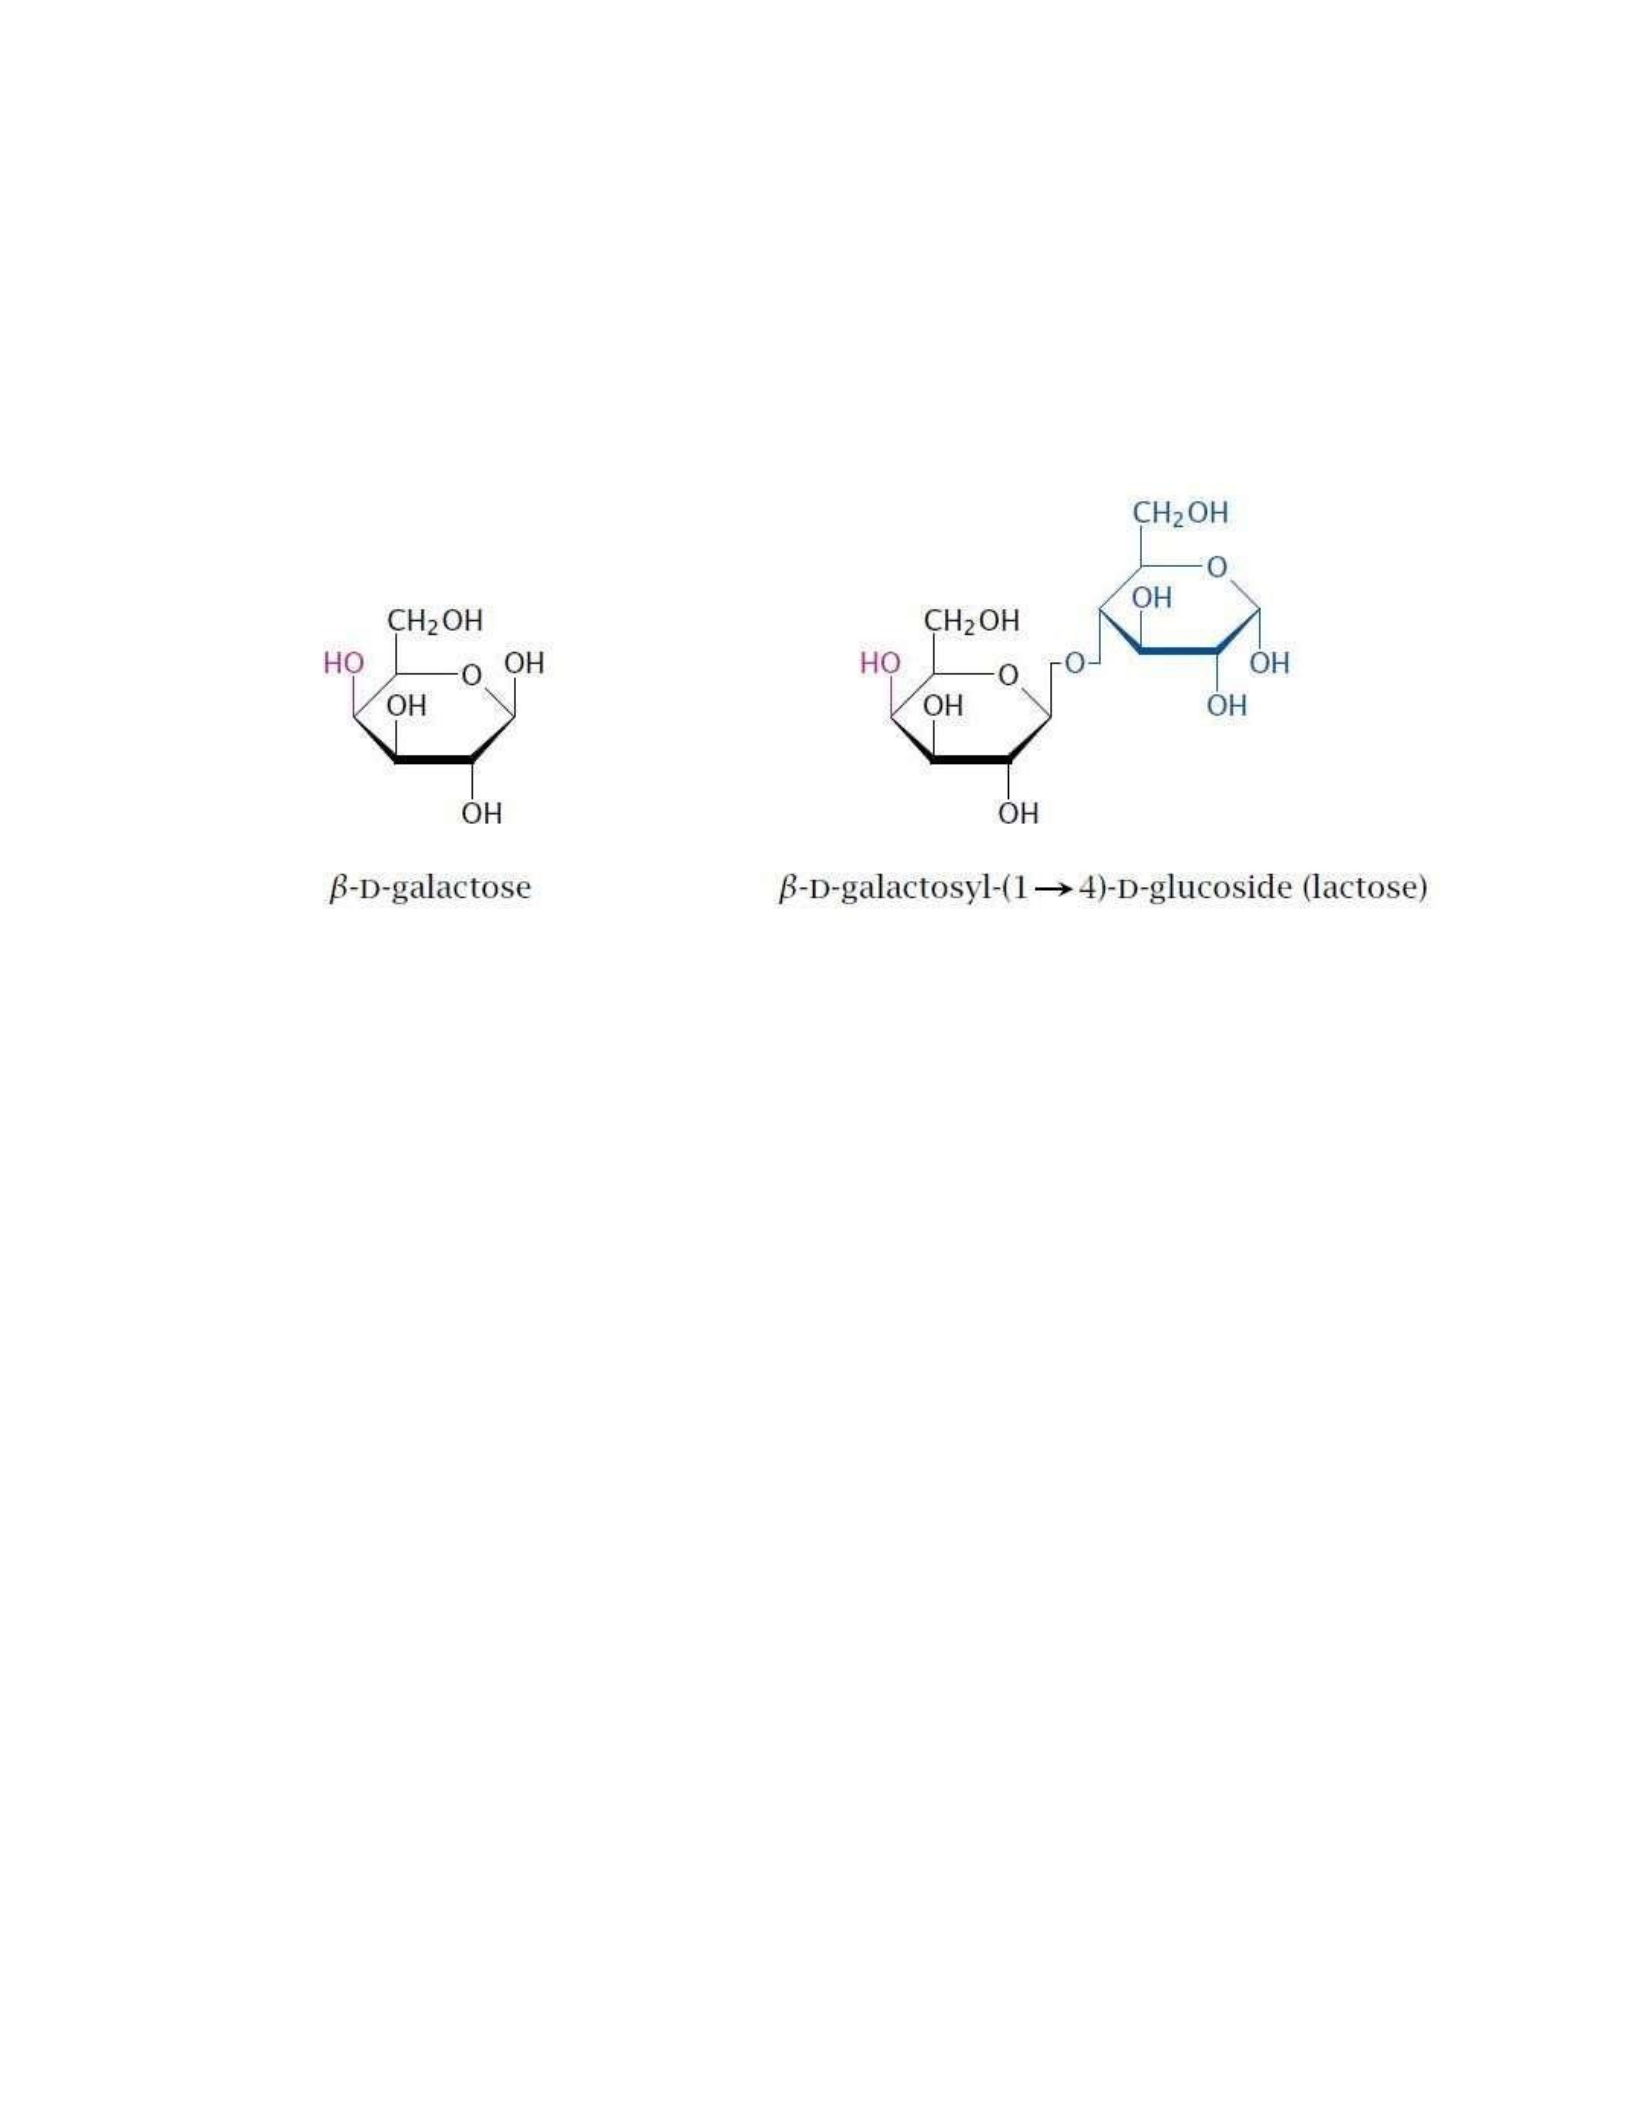
Notes: Lactose, a disaccharide of glucose and galactose, is the major carbohydrate contained in
milk. Like maltose and sucrose, it is cleaved at the brush border of the small intestine, and the
monosaccharide fragments are absorbed and passed along to the liver. The enzyme that
accomplishes the cleavage is lactase or, more precisely, β-galactosidase.
The Leloir pathway for galactose utilization
Notes: Galactose is utilized by conversion to glucose; this happens to a large extent inthe liver,
but the pathway is active in other tissues as well. The sugar is first phosphorylated by
galactokinase. The resulting galactose-1-phosphate undergoes an exchange reaction with UDP-
glucose, which is catalyzed by galactose-1-phosphate uridyltransferase and releases glucose-1-
phosphate and UDP- galactose. Glucose-1-phosphate can be converted by phosphoglucomutase to
glucose-6-phosphate, which is the first intermediate in glycolysis. UDP-galactose is converted to
UDP-glucose by UDP- galactose epimerase.
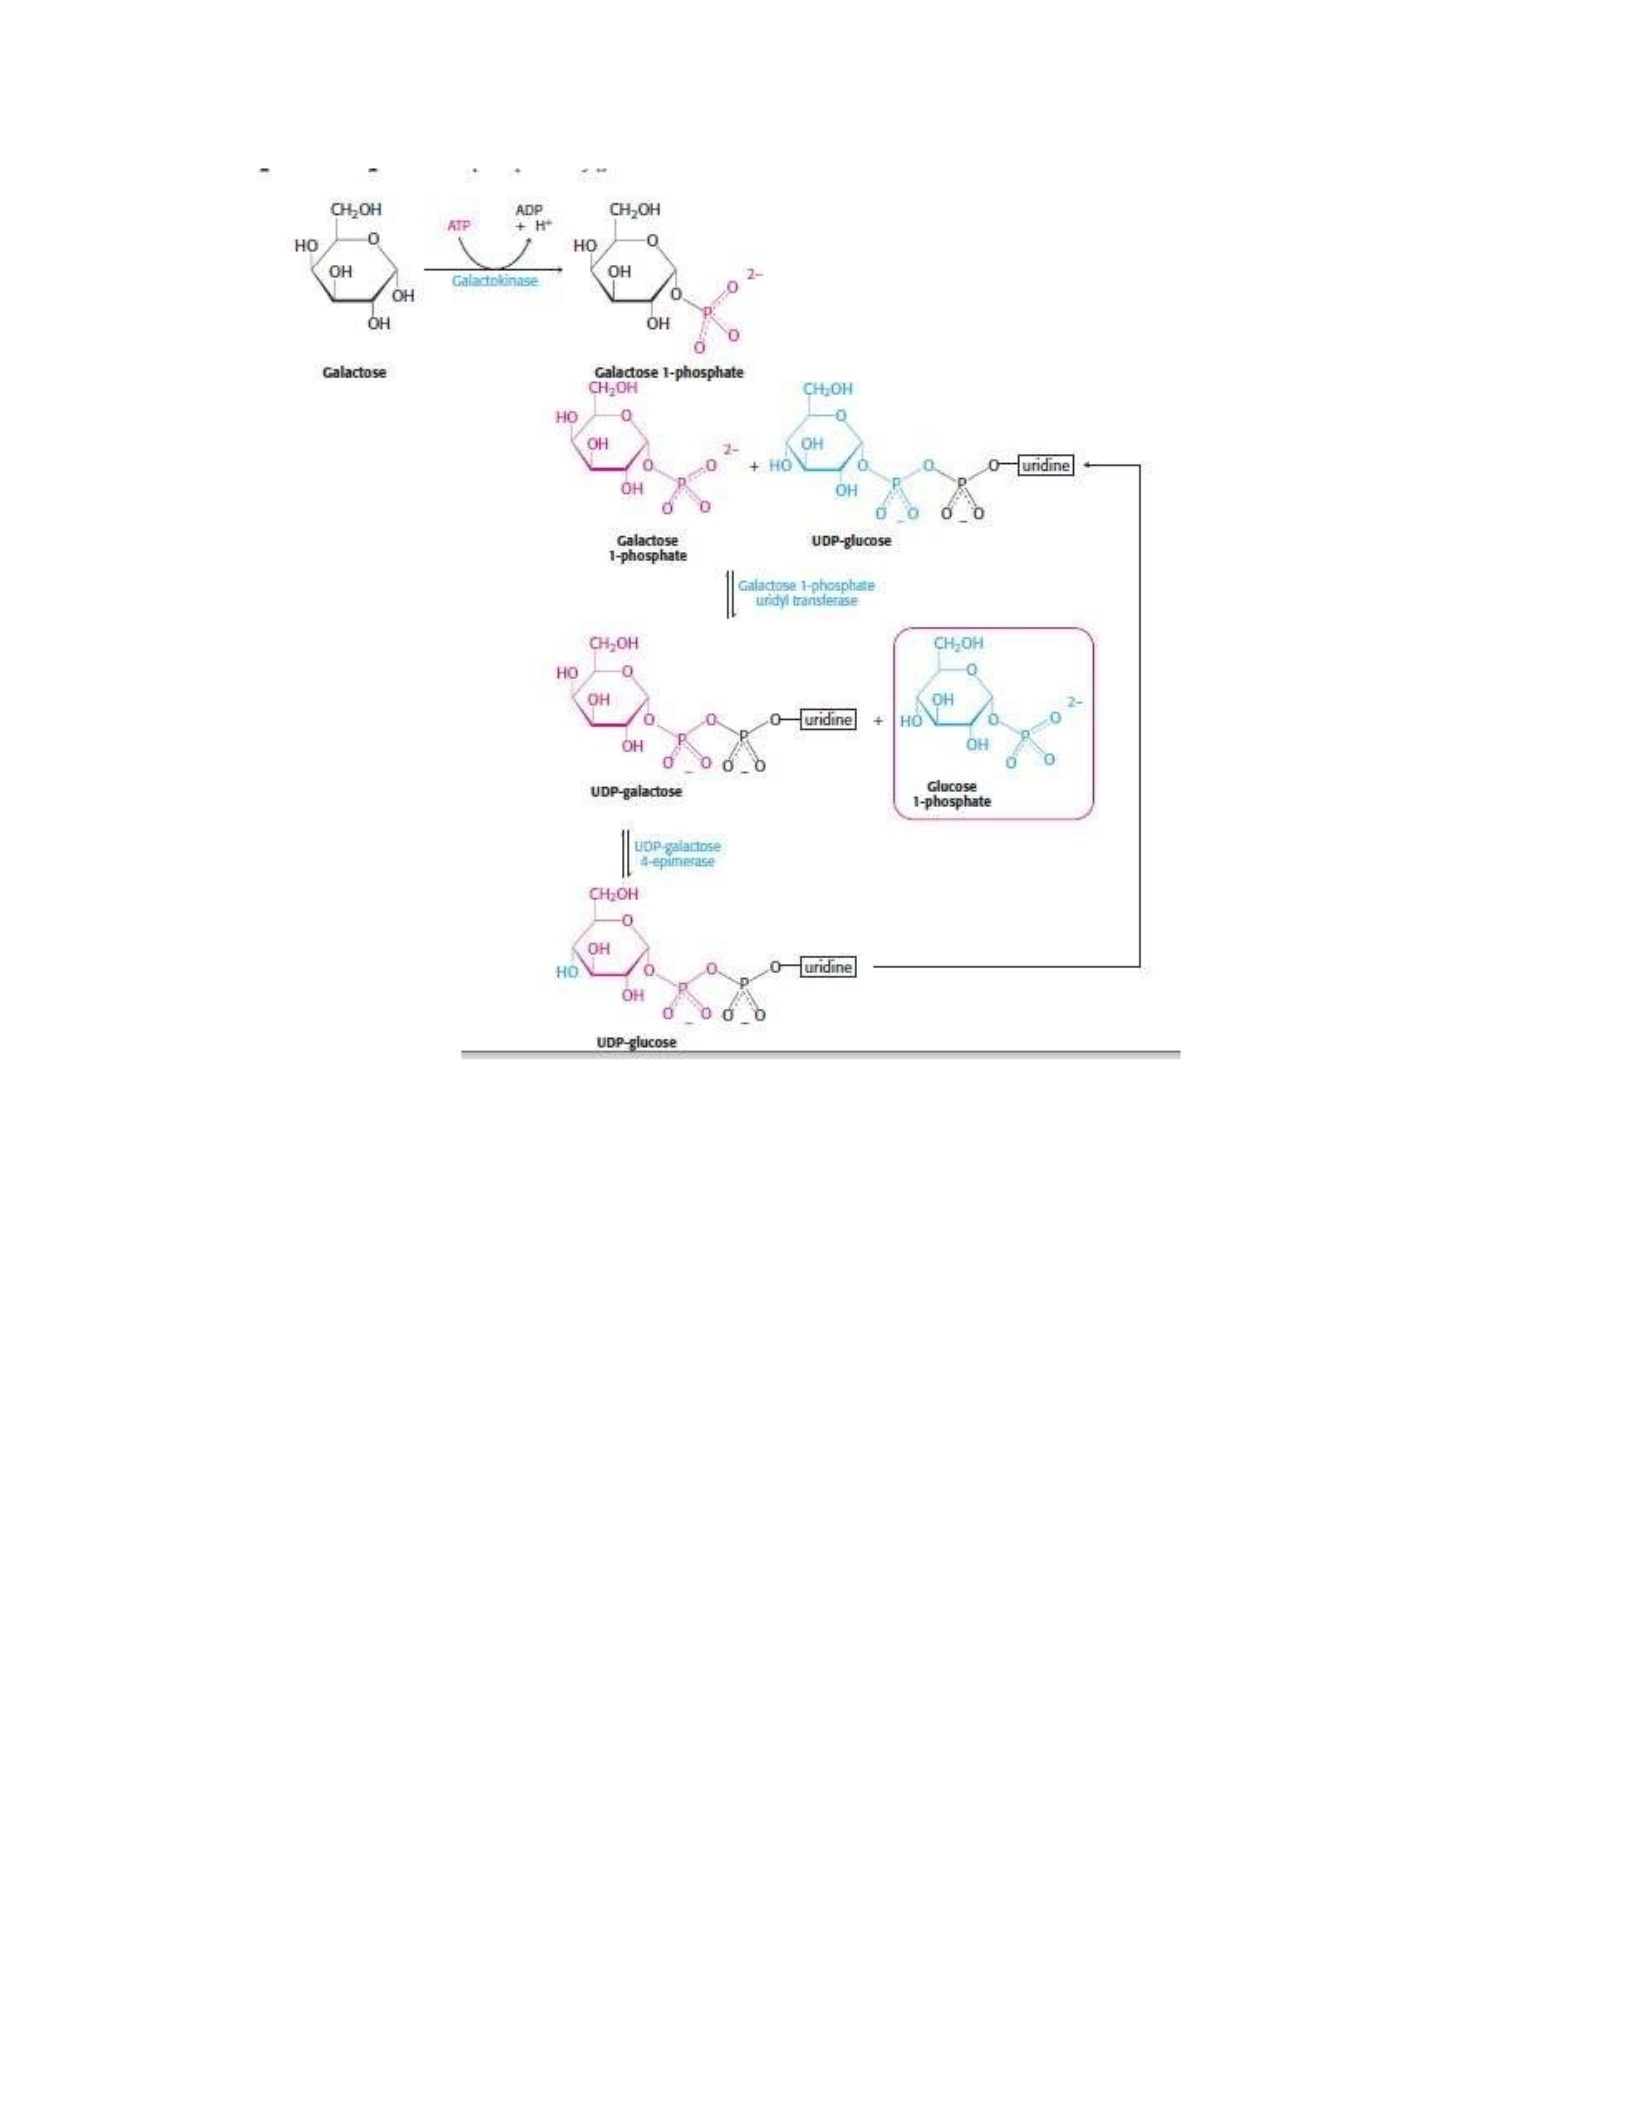
In this pathway, UDP-glucose and UDP-galactose fulfill catalytic roles but are not subject to any
net turnover, much like the intermediates in the citric acid cycle. It may therefore be said that
they form a tiny metabolic cycle between the two of them. Also note that, save for the final
epimerase reaction, the pathway is really just smoke and mirrors— performing the epimerization
on galactose directly would accomplish the same net effect, without being chemically more
difficult in any way.
Lactose intolerance
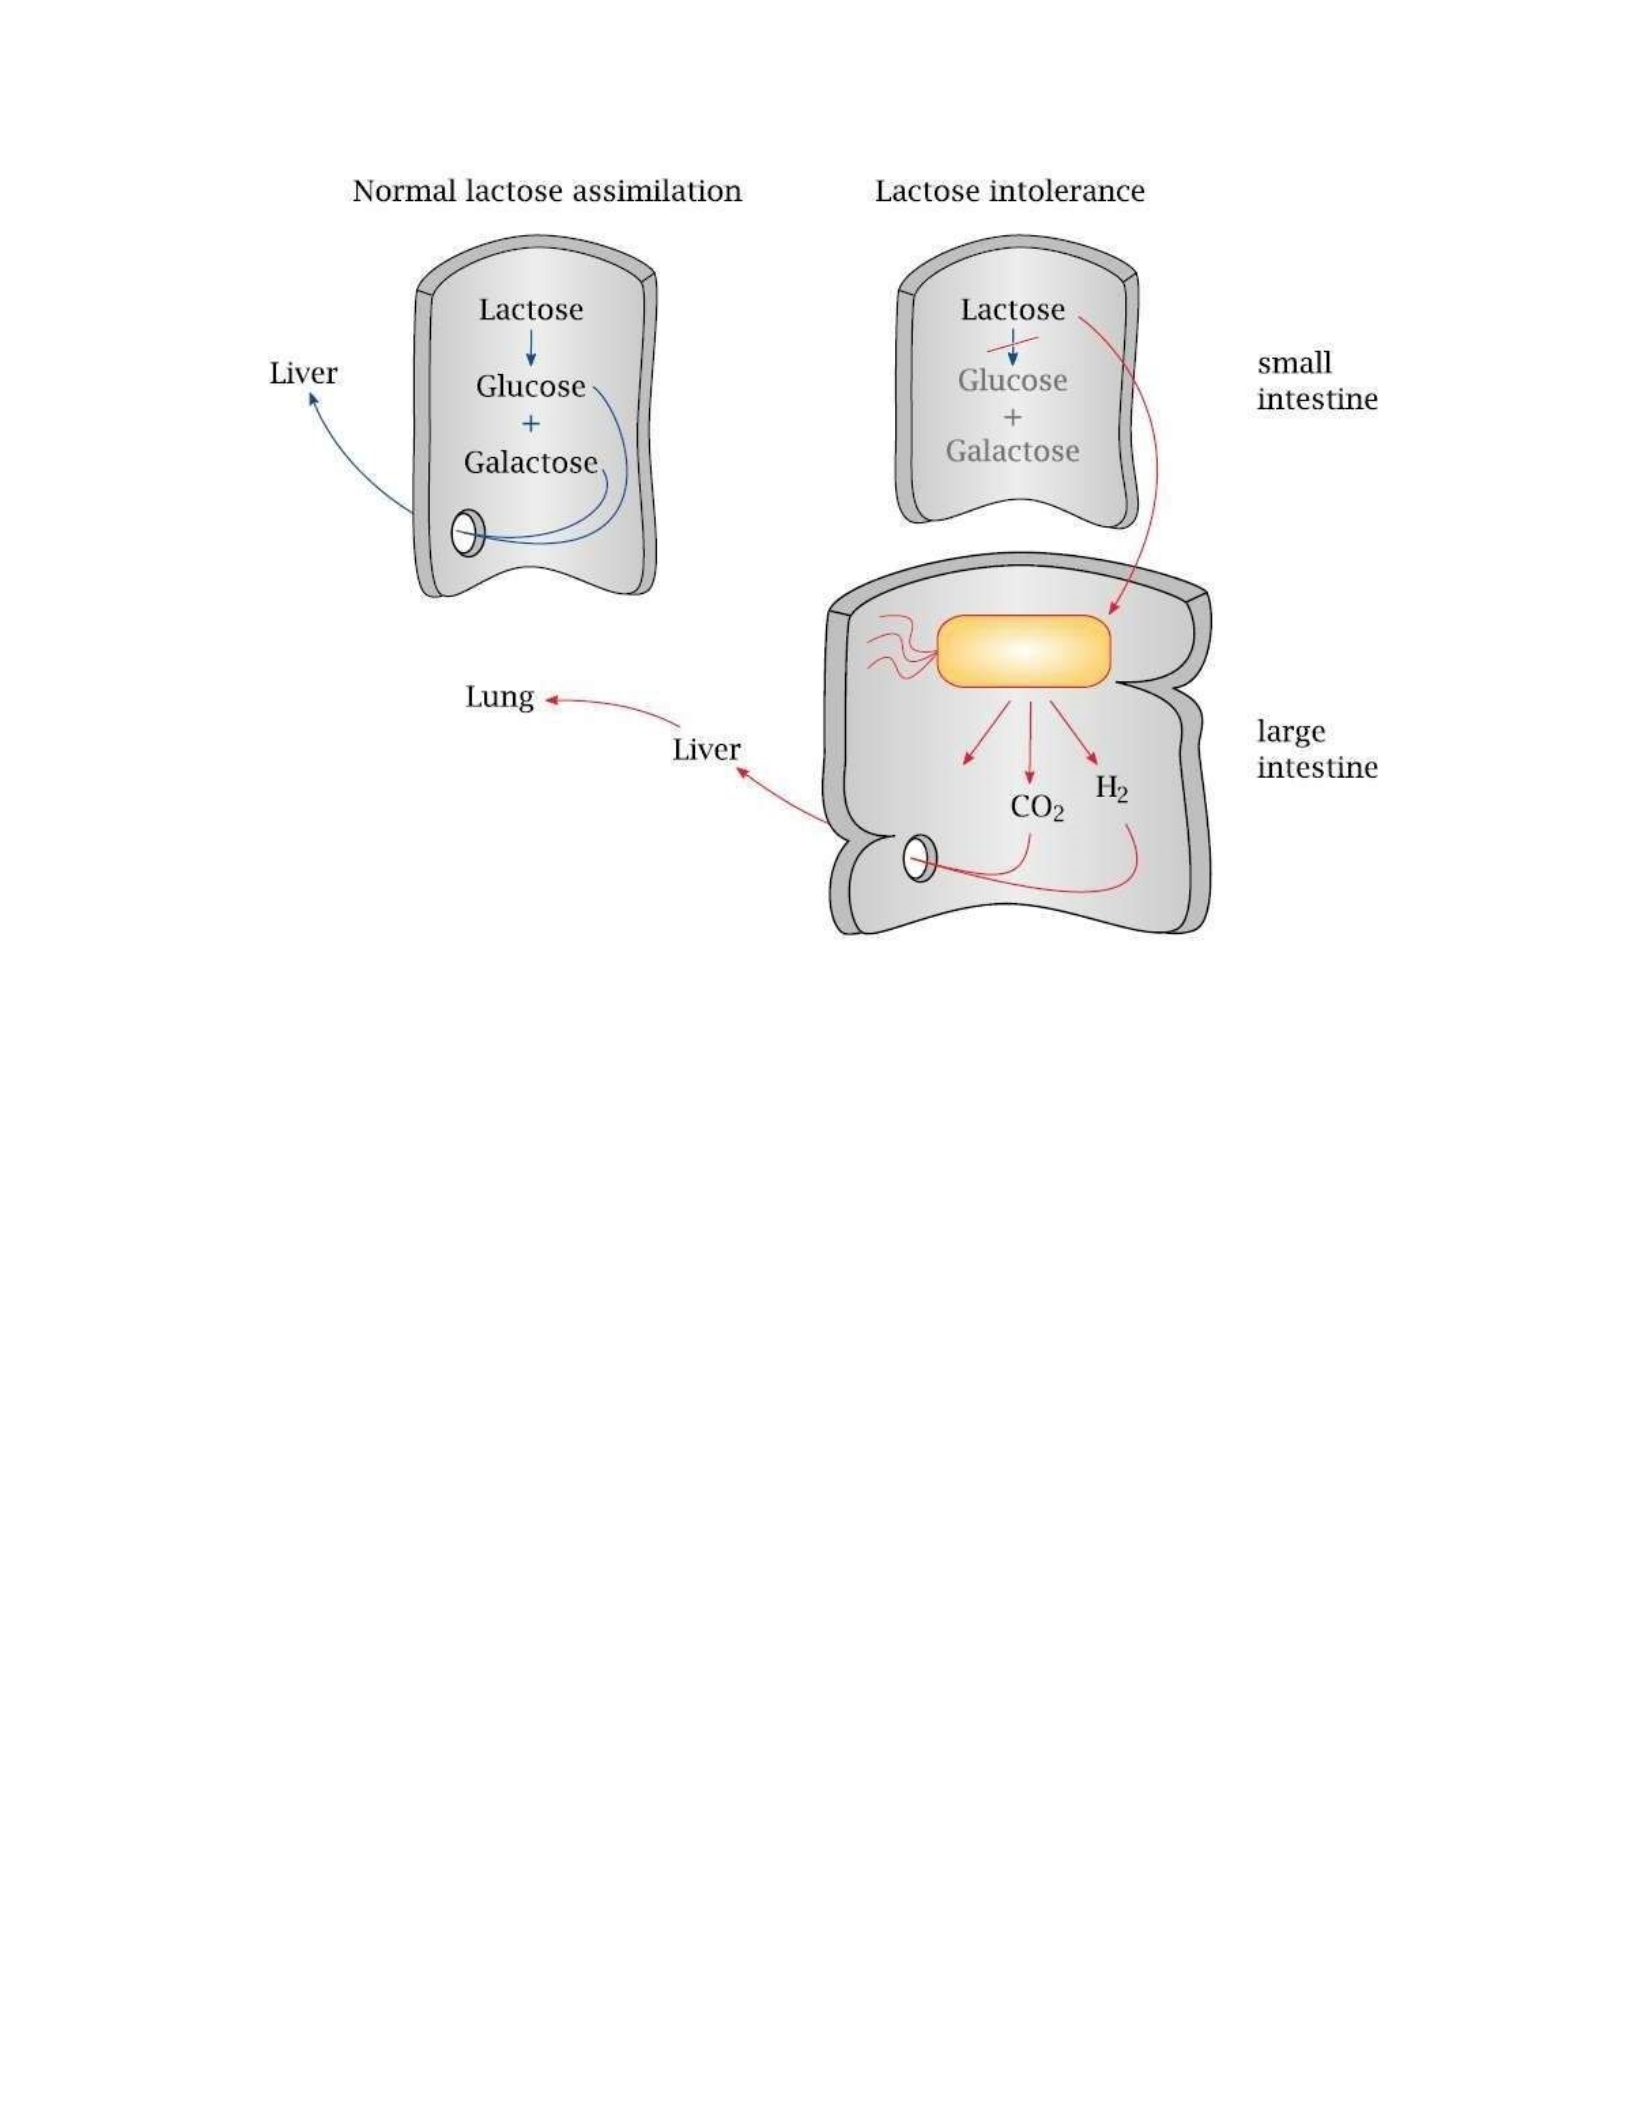
Notes: A deficiency of lactase enzyme in the small intestine gives rise to a condition named
lactose intolerance, which is found frequently in people of East Asian descent who are past their
infant age.
If lactose is not cleaved, it cannot be absorbed, so it travels down the drain from the small into
the large intestine. Many of the bacteria found there have the capacity to metabolize lactose,
which they will happily convert to acids and gas. For example, Escherichia coli has a pathway
called mixed acid fermentation. One of the products of this fermentation is formic acid
(HCOOH), which is then cleaved by formic acid lyase to H2 and CO2. This cleavage of formic
acid serves the same purpose as does ethanolic fermentation in yeast, namely, the removal of
excess acidity resulting from the fermentation. The aberrant fermentations and gas formation
lead to abdominal discomfort and diarrhea. Since the environment in the large intestine lacks
oxygen, H2 generated in the bacterial fermentation is not oxidized but instead enters the system
as such and is mostly exhaled. An increase in exhaled hydrogen gas provoked by ingestion of
lactose can be used to diagnose the condition.
Treatment consists in omission of lactose in the diet. Milk can be pre-treated with purified
bacterial β-galactosidase, rendering it suitable for consumption by lactose intolerant individuals.
Fermented milk products such as yogurt and cheese are depleted of lactose by microbial
fermentation and therefore do not pose a problem for lactose intolerant individuals.
Galactosemia

Notes: Three different enzyme deficiencies in the pathway are subsumed under the name
galactosemia, which means “galactose in the blood.” All of these are rare; type I is the most
common and most severe form. Here, the deficient enzyme is galactose- 1-phosphate
uridyltransferase. This leads to a buildup of galactose-phosphate, but also of several other
metabolites. The disease becomes manifest acutely in newborns with acute liver failure and is
deadly if not promptly diagnosed and treated. In many countries, this enzyme defect is part of
neonatal screening programs. Therapy consists in the removal of galactose from the diet, but
even so organ damage develops, mostly commonly affecting the CNS and, in girls, the ovaries.
The residual pathology that develops in spite of the diet is ascribed to the endogenous synthesis
of galactose, which proceeds via UDP-glucose and UDP-galactose; the UDP-galactose
epimerase reaction is reversible.
For a long while, it was assumed that accumulation of galactose-1-phosphate and phosphate
depletion are responsible for cell and organ damage, which is analogous to the pathogenic
mechanism in fructose intolerance. However, this assumption has been thrown into question by
the results of animal experiments. When galactose-1-uridyltransferase is genetically knocked out
in mice, these develop a profile of metabolite accumulation that closely resembles human
patients, but they do not display any of the pathology observed in humans. What is more, some
rare human cases have been reported that show the usual biochemical manifestations, but no
clinical signs. The quest for the true cause of the pathology affecting most human patients
continues.
In the order of the pathway, type II galactosemia comes first, as it involves a defect of
galactokinase. In this case, galactose simply does not enter the Leloir pathway at all; it builds up
in the blood and is mostly eliminated in the urine. The liver will not be adversely affected.
However, there is a common complication elsewhere, namely cataract, that is, obfuscation of the
lens of the eye. This is due to the reduction of galactose to galactitol in this organ by aldose
reductase.
The rarest form of galactosemia is due to the defect of UDP-galactose epimerase. The
biochemical pattern is similar to type I, except that UDP-galactose also accumulates, and as in
type I, developmental delay seems to occur. In this condition, both the utilization and the
synthesis of galactose are inhibited, and it appears necessary to maintain a low level of dietary
galactose to supply the synthesis of glycolipids and proteins.
Fructose intolerance
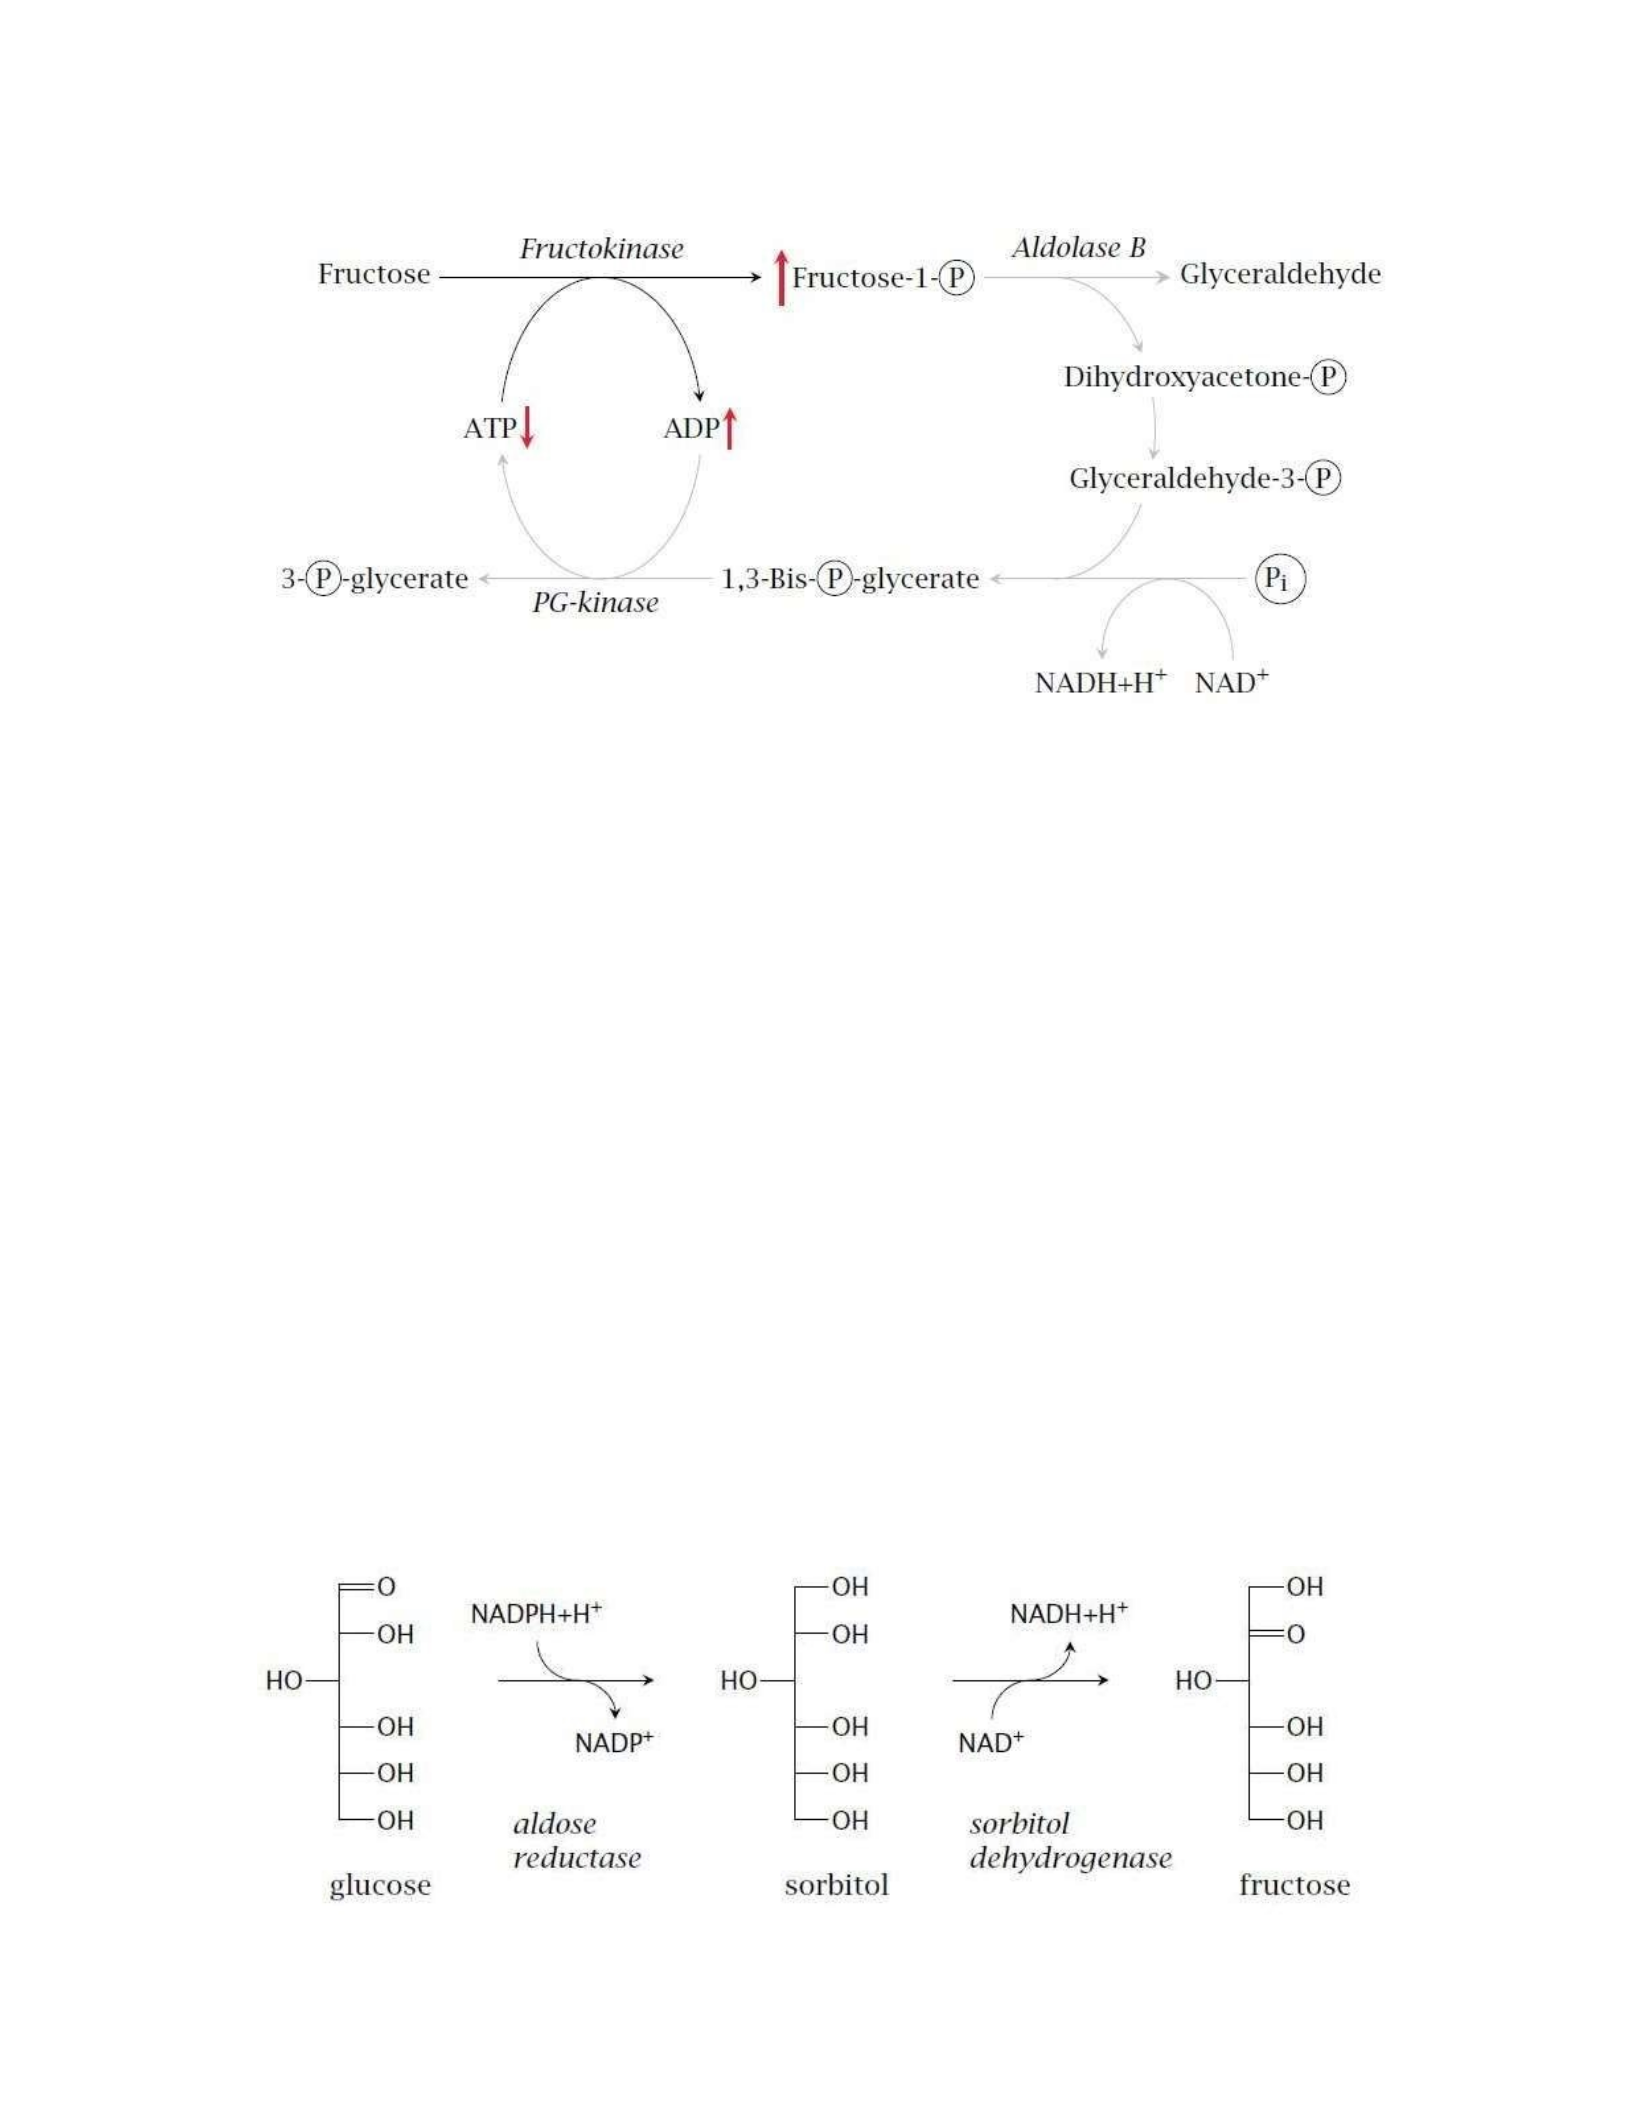
Notes: Fructose intolerance is a hereditary disease caused by a homozygous defect in the
aldolase B gene. In this condition, fructose is still phosphorylated by fructokinase. The resulting
fructose- 1-phosphate, however, cannot be processed further, and therefore the phosphate tied up
in it cannot be reclaimed. Since phosphate is required for the regeneration of ATP from ADP, this
means that ATP will be lacking, too, which will sooner or later damage or even destroy the cell.
The disease is characterized by potentially severe liver failure.
Fructose, alone or in combination with glucose, has been used in the past in the intravenous
nutrition of intensive care patients; the perceived advantage of this treatment was the insulin-
independent utilization of fructose. However, large intravenous dosages of fructose can
significantly deplete liver ATP; apparently, under heavy load, aldolase B may be unable to keep
up with fructose kinase. Fructose is no longer a major component of intravenous nutrition
schemes.
A defect in the gene encoding fructokinase leads to a condition named fructosemia or fructosuria.
As these names suggest, fructose levels are increased both in the blood and the urine. Since
fructose is not phosphorylated, no phosphate depletion occurs, and the liver cells do not incur
any damage. The disease is therefore quite benign.
Sorbitol is an intermediate of the polyol pathway
Notes: Sorbitol is not strictly a sugar, since it lacks a keto or aldehyde group. It is normally a
minor component of dietary carbohydrates, but it is also prepared semi-synthetically and used as

a sweetener. In addition, it is formed in our own metabolism from glucose in the polyol pathway,
which then converts it further to fructose. Note the use of NADPH in the first step and of NAD+
in the second, which drives the pathway in the indicated direction.
The first enzyme, aldose reductase, is not specific for glucose but can also reduce galactose, which gives
rise to galactitol. As stated above, the elevated level of galactose in the blood causes galactitol to
accumulate in the lens; the same occurs with glucose and sorbitol in insufficiently treated diabetes
mellitus. Accumulation The metabolism of glucose in mammals is limited by the rate of glucose
uptake into cells and its phosphorylation by hexokinase. Glucose uptake from the blood is
mediated by the GLUT family of glucose transporters. The transporters of hepatocytes (GLUT1,
GLUT2) and of brain neurons
(GLUT3) are always present in plasma membranes. In contrast, the main glucose transporter in
the cells of skeletal muscle, cardiac muscle, and adipose tissue (GLUT4) is sequestered in small
intracellular vesicles and moves into the plasma membrane only in response to an insulin signal.
Thus in skeletal muscle, heart, and adipose tissue, glucose uptake and metabolism depend on the
normal release of insulin by pancreatic cells in response to elevated blood glucose.
Individuals with type 1 diabetes mellitus (also called insulin-dependent diabetes) have too few
cells and cannot release sufficient insulin to trigger glucose uptake by the cells of skeletal
muscle, heart, or adipose tissue. Thus, after a meal containing carbohydrates, glucose
accumulates to abnormally high levels in the blood, a condition known as hyperglycemia.
Unable to take up glucose, muscle and fat tissue use the fatty acids of stored triacylglycerols as
their principal fuel.
In the liver, acetyl-CoA derived from this fatty acid breakdown is converted to “ketone bodies”—
acetoacetate and-hydroxybutyrate—which are exported and carried to other tissues to be used as
fuel. These compounds are especially critical to the brain, which uses ketone bodies as
alternative fuel when glucose is unavailable. (Fatty acids cannot pass through the blood-brain
barrier and thus are not a fuel for brain neurons.) In untreated type 1 diabetes, overproduction of
acetoacetate and -hydroxybutyrate leads to their accumulation in the blood, and the consequent
lowering of blood pH produces ketoacidosis, a life-threatening condition. Insulin injection
reverses this sequence of events: GLUT4 moves into the plasma membranes.
The metabolism of glucose in mammals is limited by the rate of glucose uptake into cells and its
phosphorylation by hexokinase. Glucose uptake from the blood is mediated by the GLUT family
of glucose transporters. The transporters of hepatocytes (GLUT1, GLUT2) and of brain neurons
(GLUT3) are always present in plasma membranes. In contrast, the main glucose transporter in
the cells of skeletal muscle, cardiac muscle, and adipose tissue (GLUT4) is sequestered in small
intracellular vesicles and moves into the plasma membrane only in response to an insulin signal.
Thus in skeletal muscle, heart, and adipose tissue, glucose uptake and metabolism depend on the
normal release of insulin by pancreatic cells in response to elevated blood glucose.
Individuals with type 1 diabetes mellitus (also called insulin-dependent diabetes) have too few
cells and cannot release sufficient insulin to trigger glucose uptake by the cells of skeletal
muscle, heart, or adipose tissue. Thus, after a meal containing carbohydrates, glucose
accumulates to abnormally high levels in the blood, a condition known as hyperglycemia.
Unable to take up glucose, muscle and fat tissue use the fatty acids of stored triacylglycerols as
their principal fuel.
In the liver, acetyl-CoA derived from this fatty acid breakdown is converted to “ketone bodies”—
acetoacetate and-hydroxybutyrate—which are exported and carried to other tissues to be used as

fuel. These compounds are especially critical to the brain, which uses ketone bodies as
alternative fuel when glucose is unavailable. (Fatty acids cannot pass through the blood-brain
barrier and thus are not a fuel for brain neurons.) In untreated type 1 diabetes, overproduction of
acetoacetate and -hydroxybutyrate leads to their accumulation in the blood, and the consequent
lowering of blood pH produces ketoacidosis, a life-threatening condition. Insulin injection
reverses this sequence of events: GLUT4 moves into the plasma membranes.
of either causes cataract; this is ascribed to their osmotic activity, which causes cell damage
through swelling.
Like the cells in the lens, nerve cells are able to take up glucose in an insulin independent
fashion, and like cataract, nerve cell damage (diabetic polyneuropathy) is a common long-term
complication in diabetes. It appears plausible that sorbitol accumulation might also be
responsible for this nerve cell damage. Inhibitors of aldose reductase have been developed and
have shown promise in animal models of both diabetes and galactosemia, but evidence of
clinical effectiveness in humans is scarce.
Conversion of glucose to fructose via the polyol pathway occurs in the seminal vesicles, which
part of the male sexual organs, and fructose is found in the sperm fluid. It supplies these cells
with fuel in their frantic quest for an oocyte; the advantage of this somewhat unusual source of
energy may be that fructose will not be pilfered by the other tissues the sperm fluid will get into
contact with.
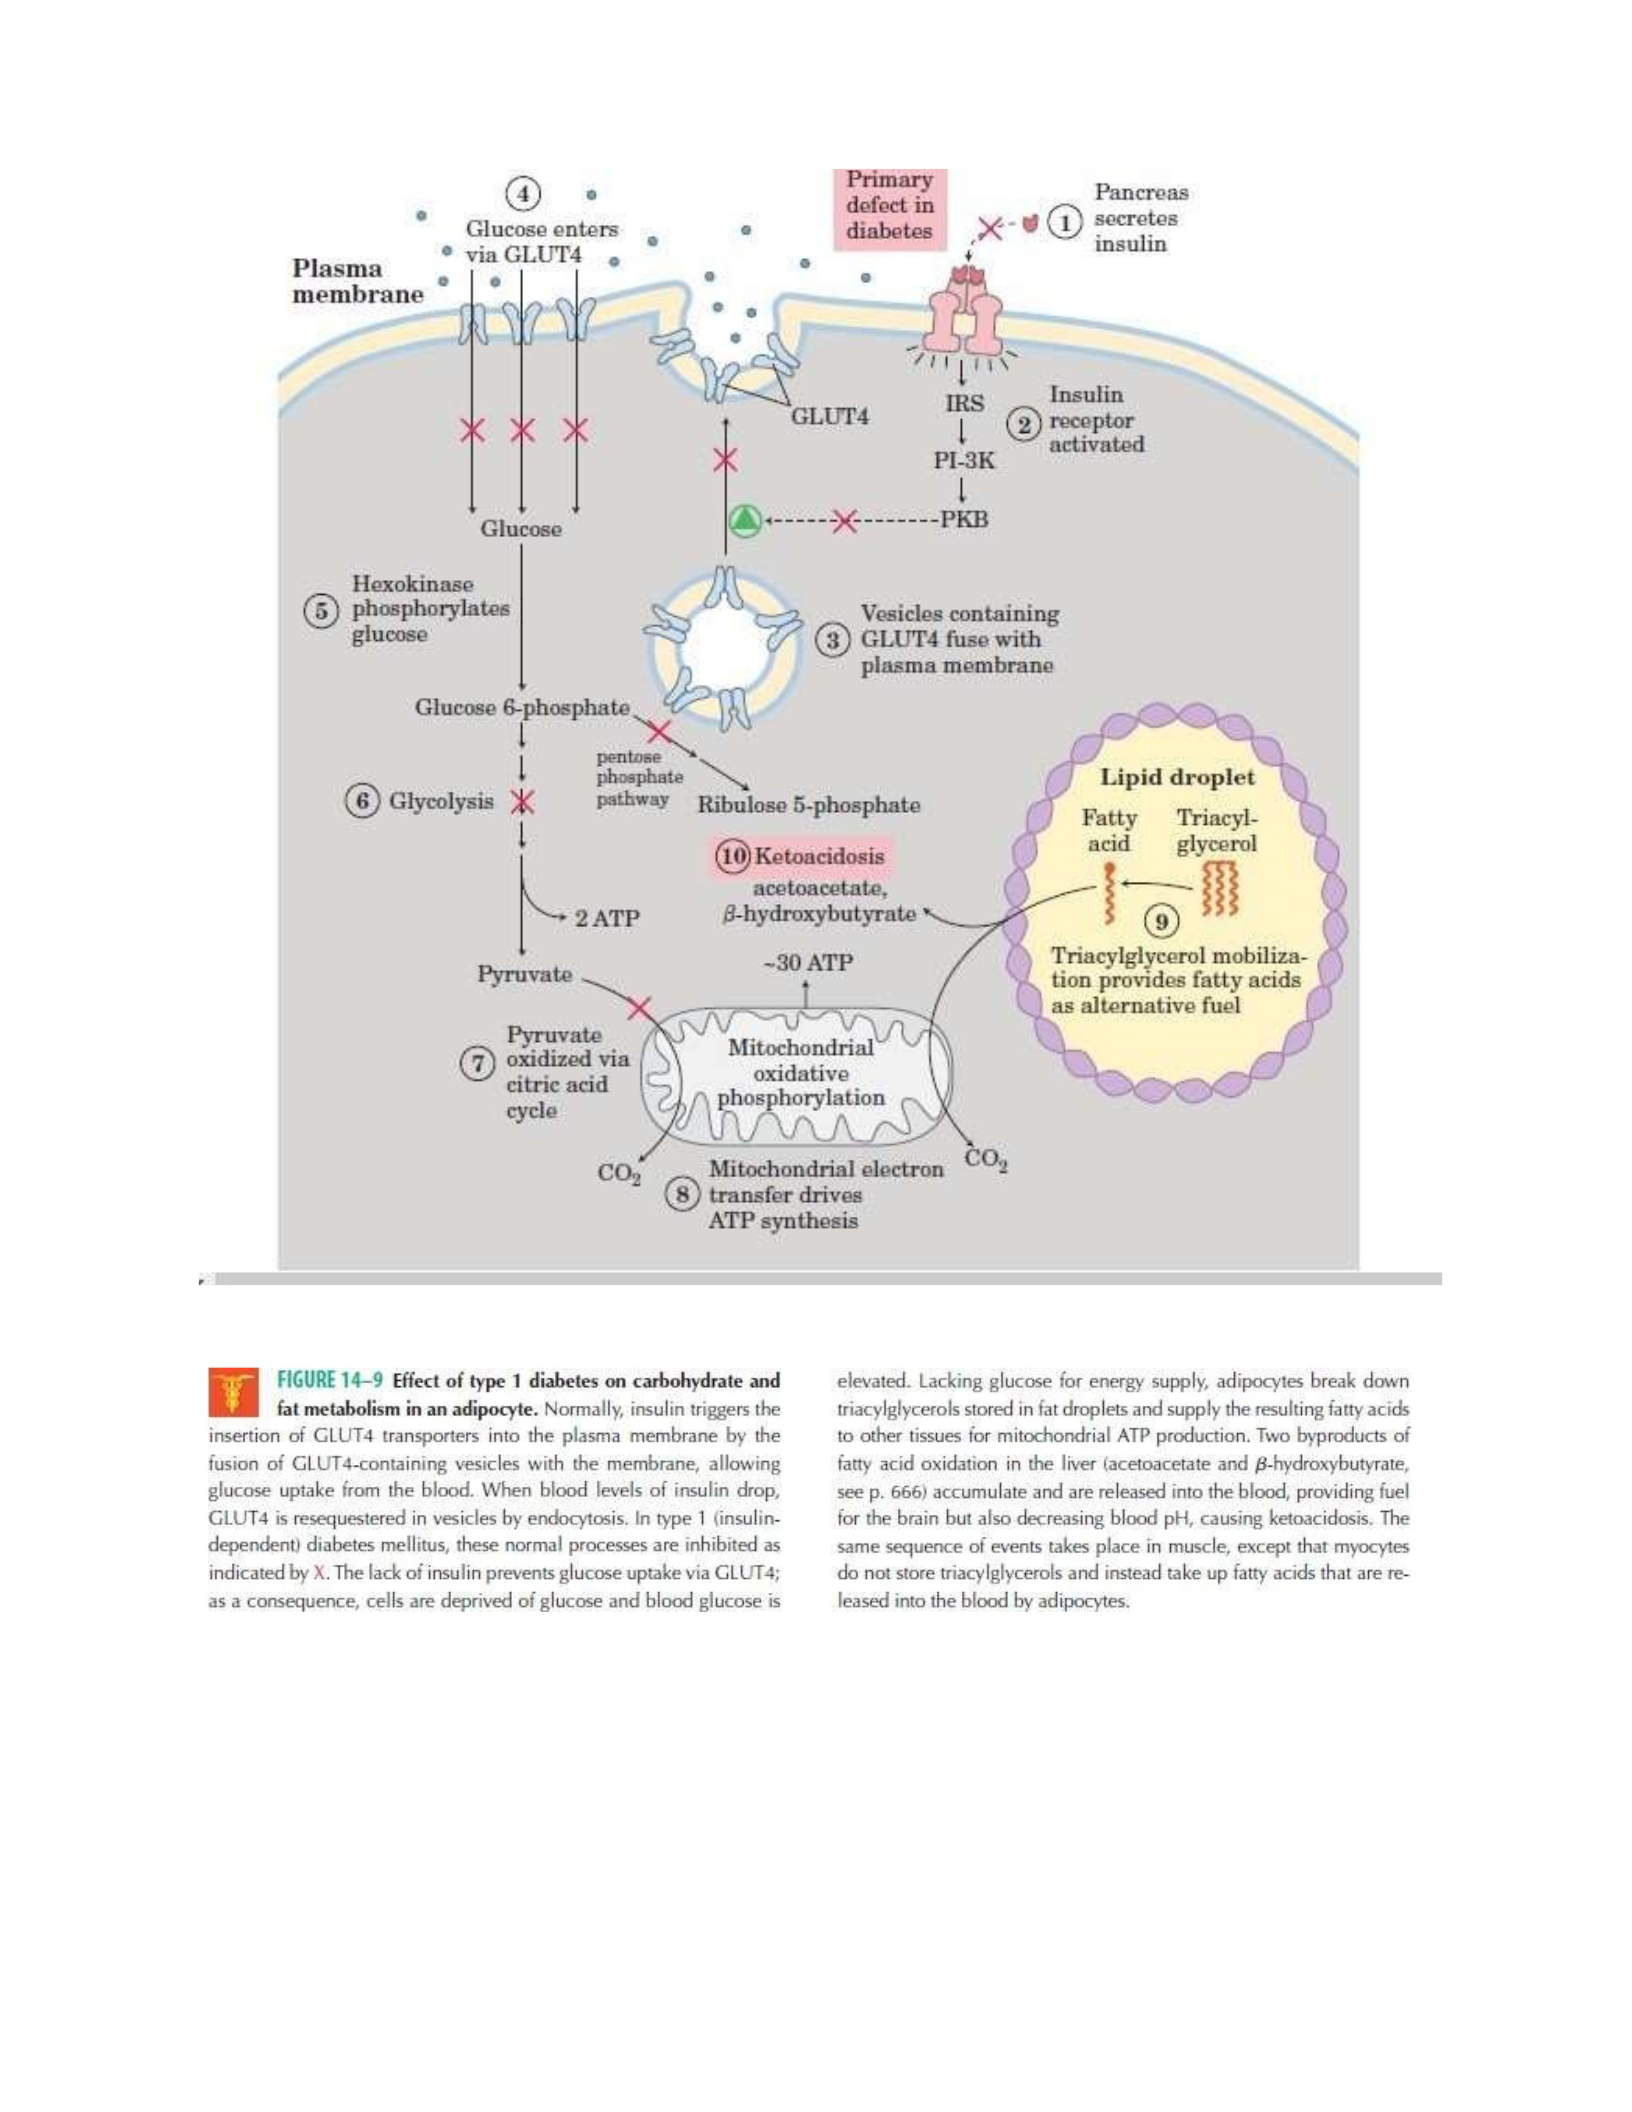
Glucose Uptake Is Deficient in Type 1 Diabetes Mellitus
The metabolism of glucose in mammals is limited by the rate of glucose uptake into cells and its
phosphorylation by hexokinase. Glucose uptake from the blood is mediated by the GLUT family
of glucose transporters. The transporters of hepatocytes (GLUT1, GLUT2) and of brain neurons
(GLUT3) are always present in plasma membranes. In contrast, the main glucose transporter in
the cells of skeletal muscle, cardiac muscle, and adipose tissue (GLUT4) is sequestered in small
intracellular vesicles and moves into the plasma membrane only in response to an insulin signal.
Thus in skeletal muscle, heart, and adipose tissue, glucose uptake and metabolism depend on the
normal release of insulin by pancreatic cells in response to elevated blood glucose.
Individuals with type 1 diabetes mellitus (also called insulin-dependent diabetes) have too few
cells and cannot release sufficient insulin to trigger glucose uptake by the cells of skeletal
muscle, heart, or adipose tissue. Thus, after a meal containing carbohydrates, glucose
accumulates to abnormally high levels in the blood, a condition known as hyperglycemia.
Unable to take up glucose, muscle and fat tissue use the fatty acids of stored triacylglycerols as
their principal fuel.
In the liver, acetyl-CoA derived from this fatty acid breakdown is converted to “ketone bodies”—
acetoacetate and-hydroxybutyrate—which are exported and carried to other tissues to be used as
fuel. These compounds are especially critical to the brain, which uses ketone bodies as
alternative fuel when glucose is unavailable. (Fatty acids cannot pass through the blood-brain
barrier and thus are not a fuel for brain neurons.) In untreated type 1 diabetes, overproduction of
acetoacetate and -hydroxybutyrate leads to their accumulation in the blood, and the consequent
lowering of blood pH produces ketoacidosis, a life-threatening condition. Insulin injection
reverses this sequence of events: GLUT4 moves into the plasma membranes.
GLYCOLYSIS AND CANCER CELLS
In many types of tumors found in humans and other animals, glucose uptake and glycolysis
proceed about 10 times faster than in normal, noncancerous tissues. Most tumor cells grow under
hypoxic conditions (i.e., with limited oxygen supply) because, at least initially, they lack the
capillary network to supply sufficient oxygen. Cancer cells located more than 100 to 200 m from
the nearest capillaries must depend on glycolysis alone (without further oxidation of pyruvate)
for much of their ATP production. The energy yield (2 ATP per glucose) is far lower than can be
obtained by the complete oxidation of pyruvate to CO2 in mitochondria (about 30 ATP per
glucose). So, to make the same amount of ATP, tumor cells must take up much more glucose than

do normal cells, converting it to pyruvate and then to lactate as they recycle NADH. It is likely
that two early steps in the transformation of a normal cell into a tumor cell are (1) the change to
dependence on glycolysis for ATP production, and (2) the development of tolerance to a low pH
in the extracellular fluid (caused by release of the end product of glycolysis, lactic acid). In
general, the more aggressive the tumor, the greater is its rate of glycolysis. This increase in
glycolysis is achieved at least in part by increased synthesis of the glycolytic enzymes and of the
plasma membrane transporters GLUT1 and GLUT3 that carry glucose into cells. (Recall that
GLUT1 and GLUT3 are not dependent on insulin.) The hypoxia-inducible transcription factor
(HIF-1) is a protein that acts at the level of mRNA synthesis to stimulate the production of at
least eight glycolytic enzymes and the glucose transporters when oxygen supply is limited. With
the resulting high rate of glycolysis, the tumor cell can survive anaerobic conditions until the
supply of blood vessels has caught up with tumor growth.
GLUCONEOGENESIS
Before we embark on the aerobic fate of pyruvate, let us discuss gluconeogenesis which utilizes
most steps of glycolysis to synthesize glucose.
GLUCONEOGENESIS
Introduction
Glucose is a key metabolite in human metabolism, but it is not always available at levels in the
diet. Therefore, a pathway exists that converts other foodstuffs into glucose. This pathway is
called gluconeogenesis.
Glucose is an indispensable metabolite
•The brain requires at least ~50% of its calories in the form of glucose • Red blood cells
exclusively subsist on glucose
•Glucose is a precursor of other sugars needed in the biosynthesis of nucleotides, glycoproteins,
and glycolipids
•Glucose is needed to replenish NADPH, which supplies reducing power for biosynthesis and
detoxification
Notes: These considerations make the need for gluconeogenesis quite clear—we just can’t afford to leave
the blood glucose level up to the vagaries of dietary supply.
Overview of gluconeogenesis
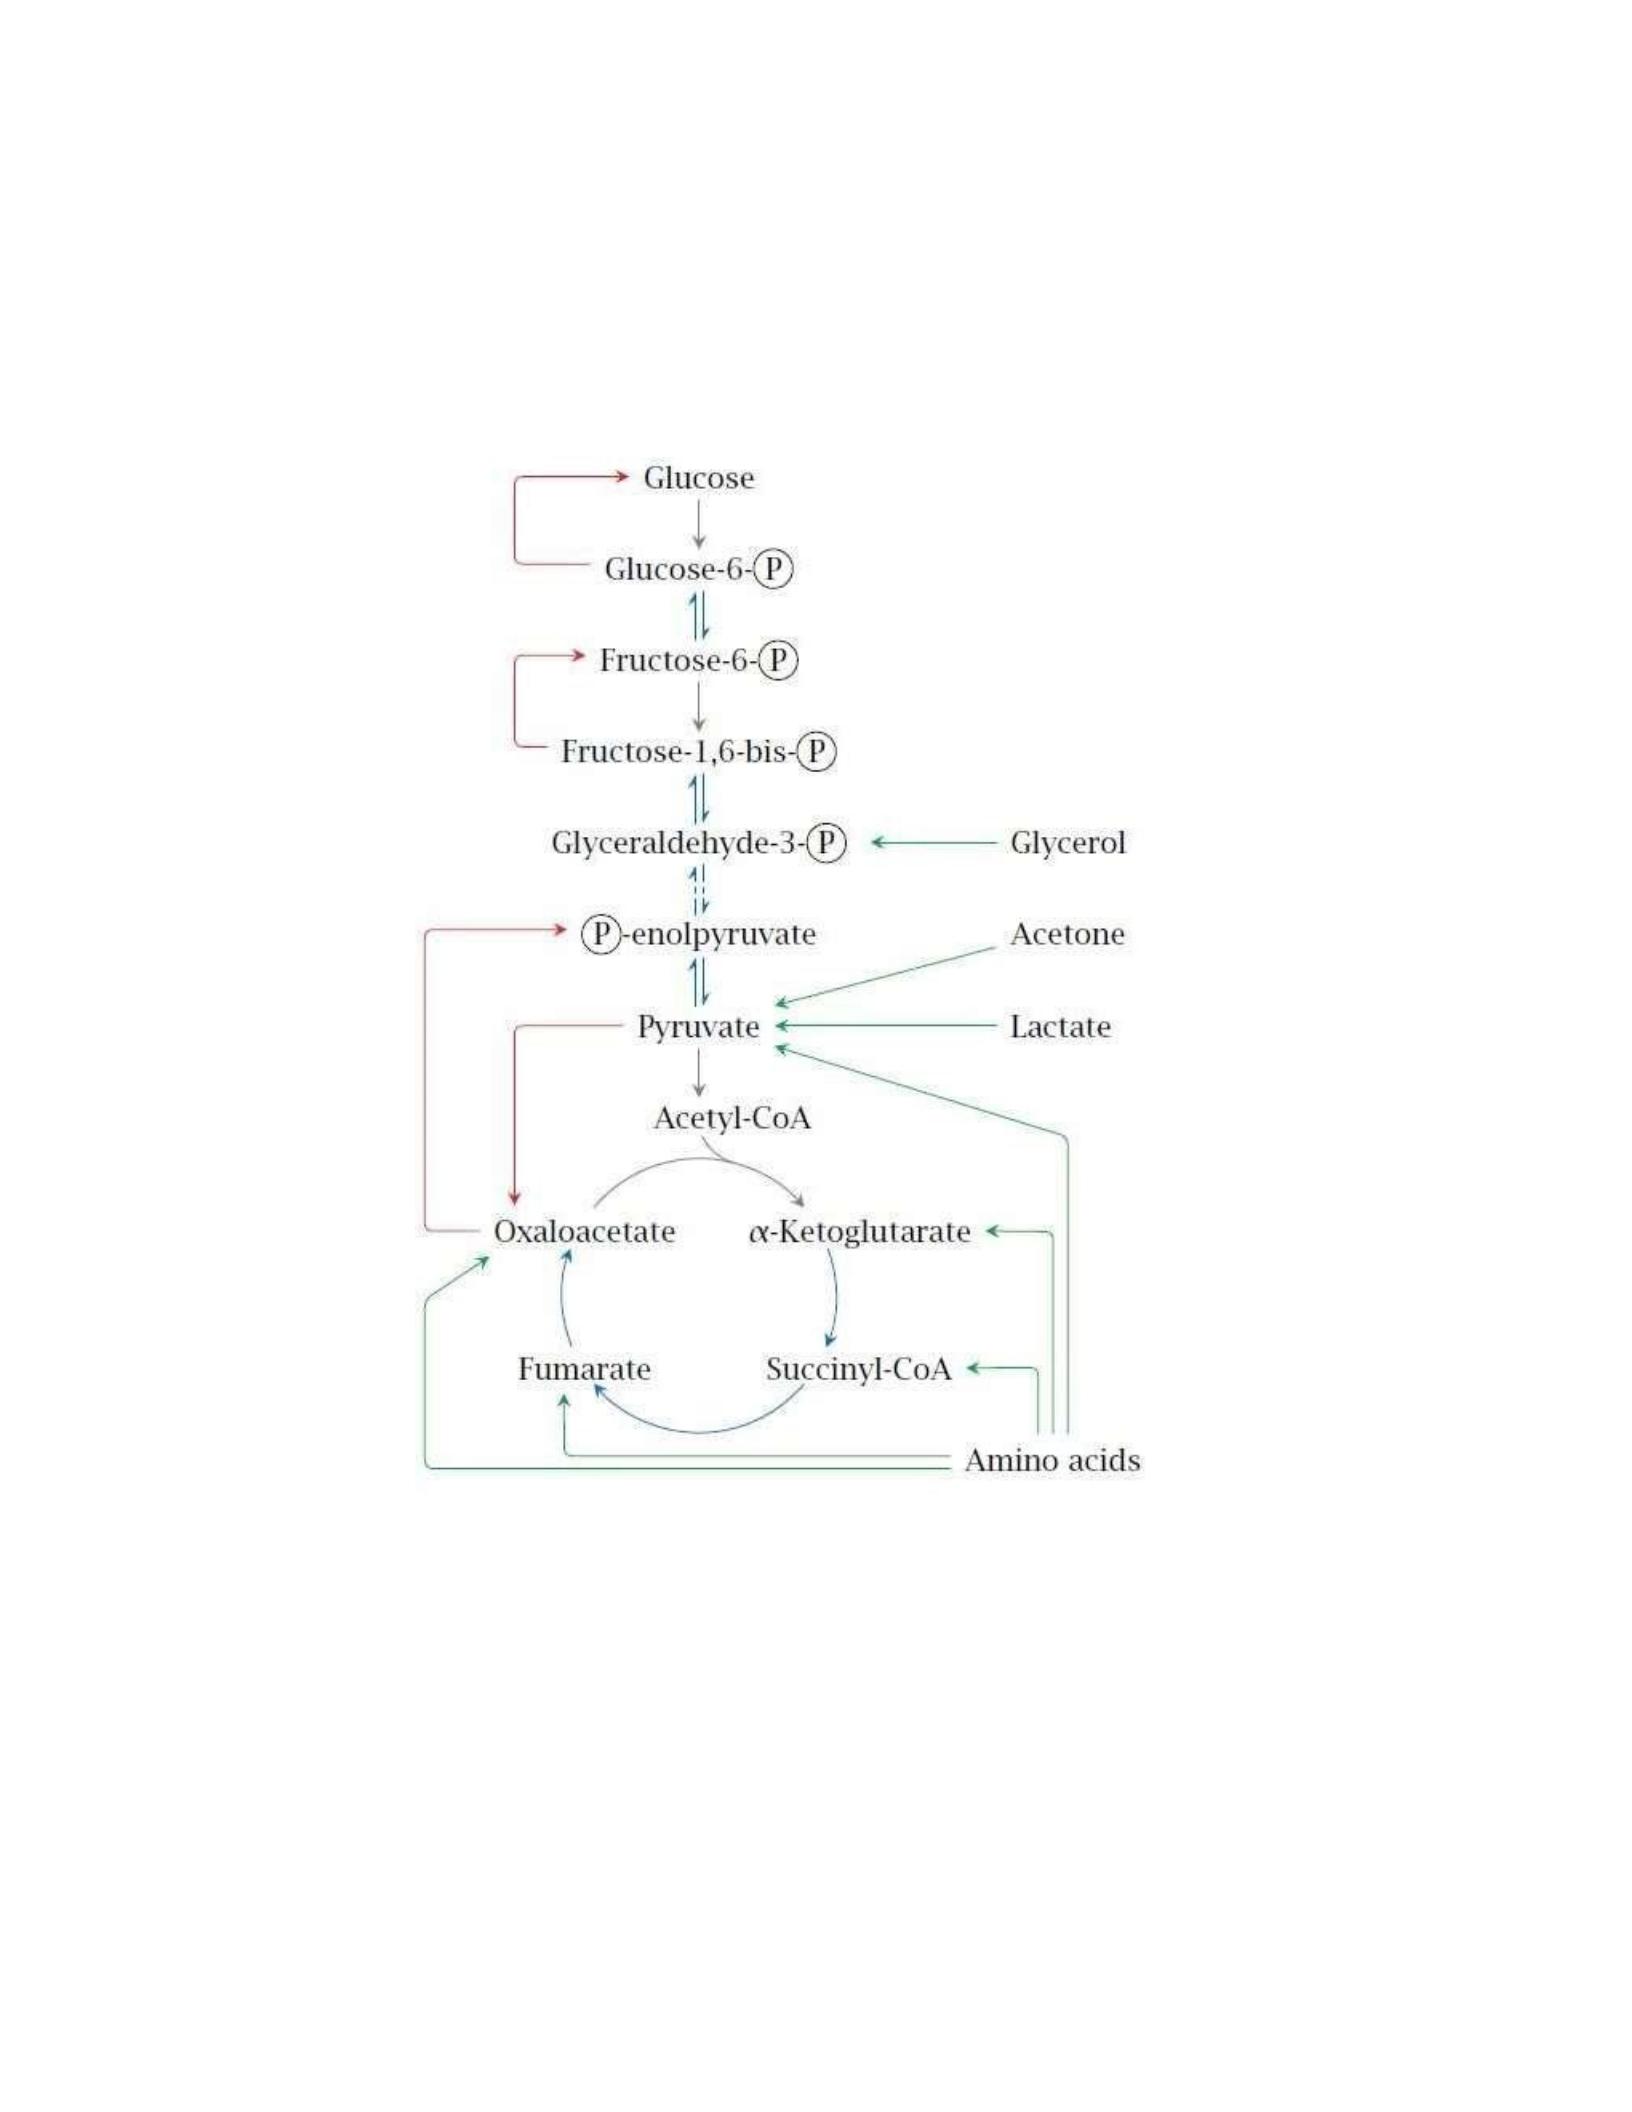
Notes: Gluconeogenesis is the reversal of glycolysis, with several workarounds for the irreversible
reactions in that pathway. In this scheme (below), the reactions that are shared between glycolysis and
gluconeogenesis are shown in blue, whereas reactions that are specific for gluconeogenesis are shown in
red. As you can see, both pyruvate and oxaloacetate are starting points for red arrows; therefore, any
pathway that yields either of these, or indeed any other intermediate of glycolysis, can supply substrate
carbon for gluconeogenesis. These pathways are indicated here by green arrows.
The major substrate supply for gluconeogenesis is protein, both dietary and endogenous. Protein is first
broken down into its constituent amino acids. Those amino acids that can be converted to pyruvate or any
of the TCA cycle intermediates can serve as substrates for gluconeogenesis, and are therefore called
glucogenic.
Leucine, lysine and the aromatic amino acids are degraded to acetyl-CoA or acetoacetate. Since
acetoacetate is a ketone body, and acetyl-CoA can be converted to ketone bodies, these amino acids are
called ketogenic. While it was believed for a long time that ketone bodies cannot be converted to glucose
in human metabolism, this is not strictly true, since the ketone body acetone can be converted to pyruvate.
Nevertheless, the contribution of ketogenic amino acids to glucose regeneration is likely minor.
Gluconeogenesis proceeds only in the liver and the kidneys, and since the liver is five times larger than
the two kidneys combined, it provides the greater share of all glucose produced. The pathway does not
occur in the brain, fat tissue, or skeletal muscle. Together with glycogen degradation, gluconeogenesis
ensures stable blood glucose levels between meals. Gluconeogenesis also enables us to maintain the
necessary glucose levels when on a diet that is rich in protein but low in carbohydrates.
Reactions in gluconeogenesis
Most reactions are shared with glycolysis, which we already know, and we here only need to consider the
small number of reactions that are specific to gluconeogenesis. The final reaction in glycolysis is the
transfer of the phosphate group from phosphoenolpyruvate (PEP) to ATP. This reaction is irreversible
because of the strongly exergonic nature of the accompanying rearrangement of pyruvate from the enol to
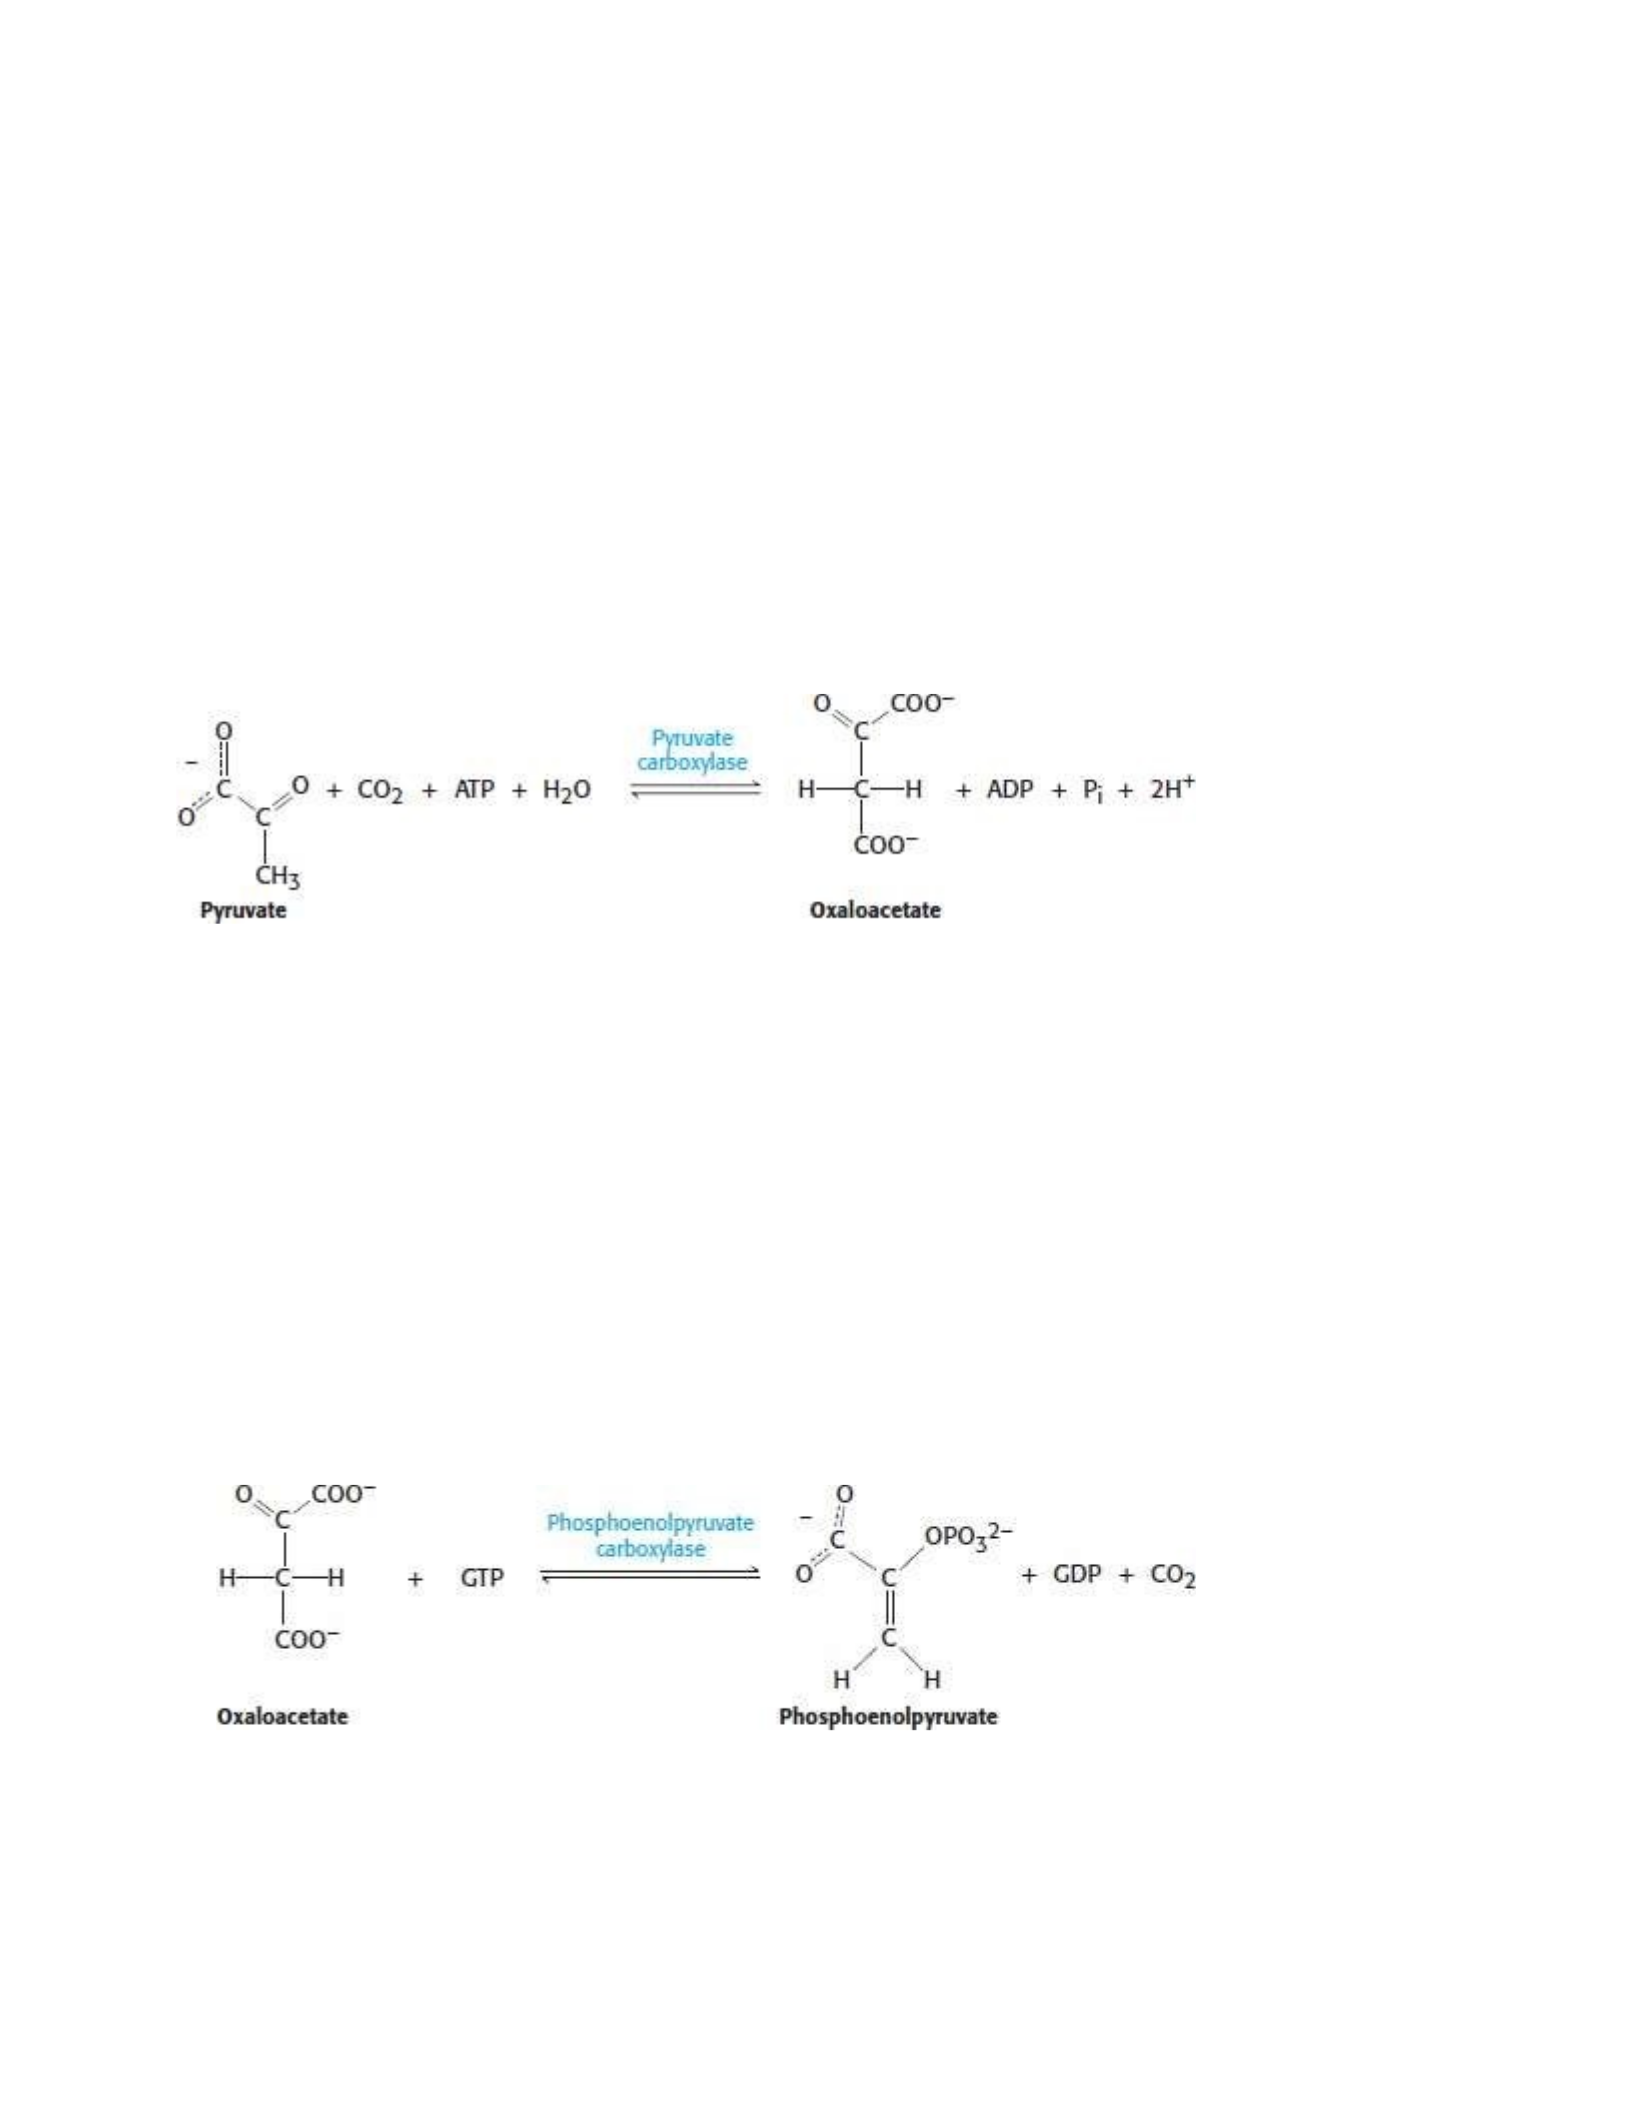
the keto form. In gluconeogenesis, it takes two enzymatic steps to turn pyruvate back into PEP, namely
(1) the carboxylation of pyruvate to oxaloacetate by pyruvate carboxylase, and (2) conversion of
oxaloacetate to PEP by phosphoenolpyruvate carboxykinase.
The pyruvate carboxylase reaction
Notes: With the pyruvate carboxylase reaction, we are able to metabolically fix CO2—
just like plants, however, it is necessary to consider that the very same molecule of CO2 gets released again
in the next step. The whole purpose of transient CO2 fixation is to enable this subsequent reaction.
The phosphoenolpyruvate carboxykinase reaction
Notes: In the phosphoenolpyruvate carboxykinase reaction, the CO2 that just had been attached to the
substrate leaves again, giving rise to an enolpyruvate anion intermediate that attacks and acquires the
terminal phosphate group of GTP. The product is phosphoenolpyruvate, which is an intermediate of
glycolysis.
Fructose-1,6-bisphosphatase and glucose-6-phosphatase
1. Fructose 6-phosphate is formed from fructose 1,6-bisphosphate by hydrolysis of the phosphate
ester at carbon 1. Fructose 1,6-bisphosphatase catalyzes this exergonic hydrolysis.
2. Glucose is formed by the hydrolysis of glucose 6-phosphate in a reaction catalyzed by glucose
6phosphatase
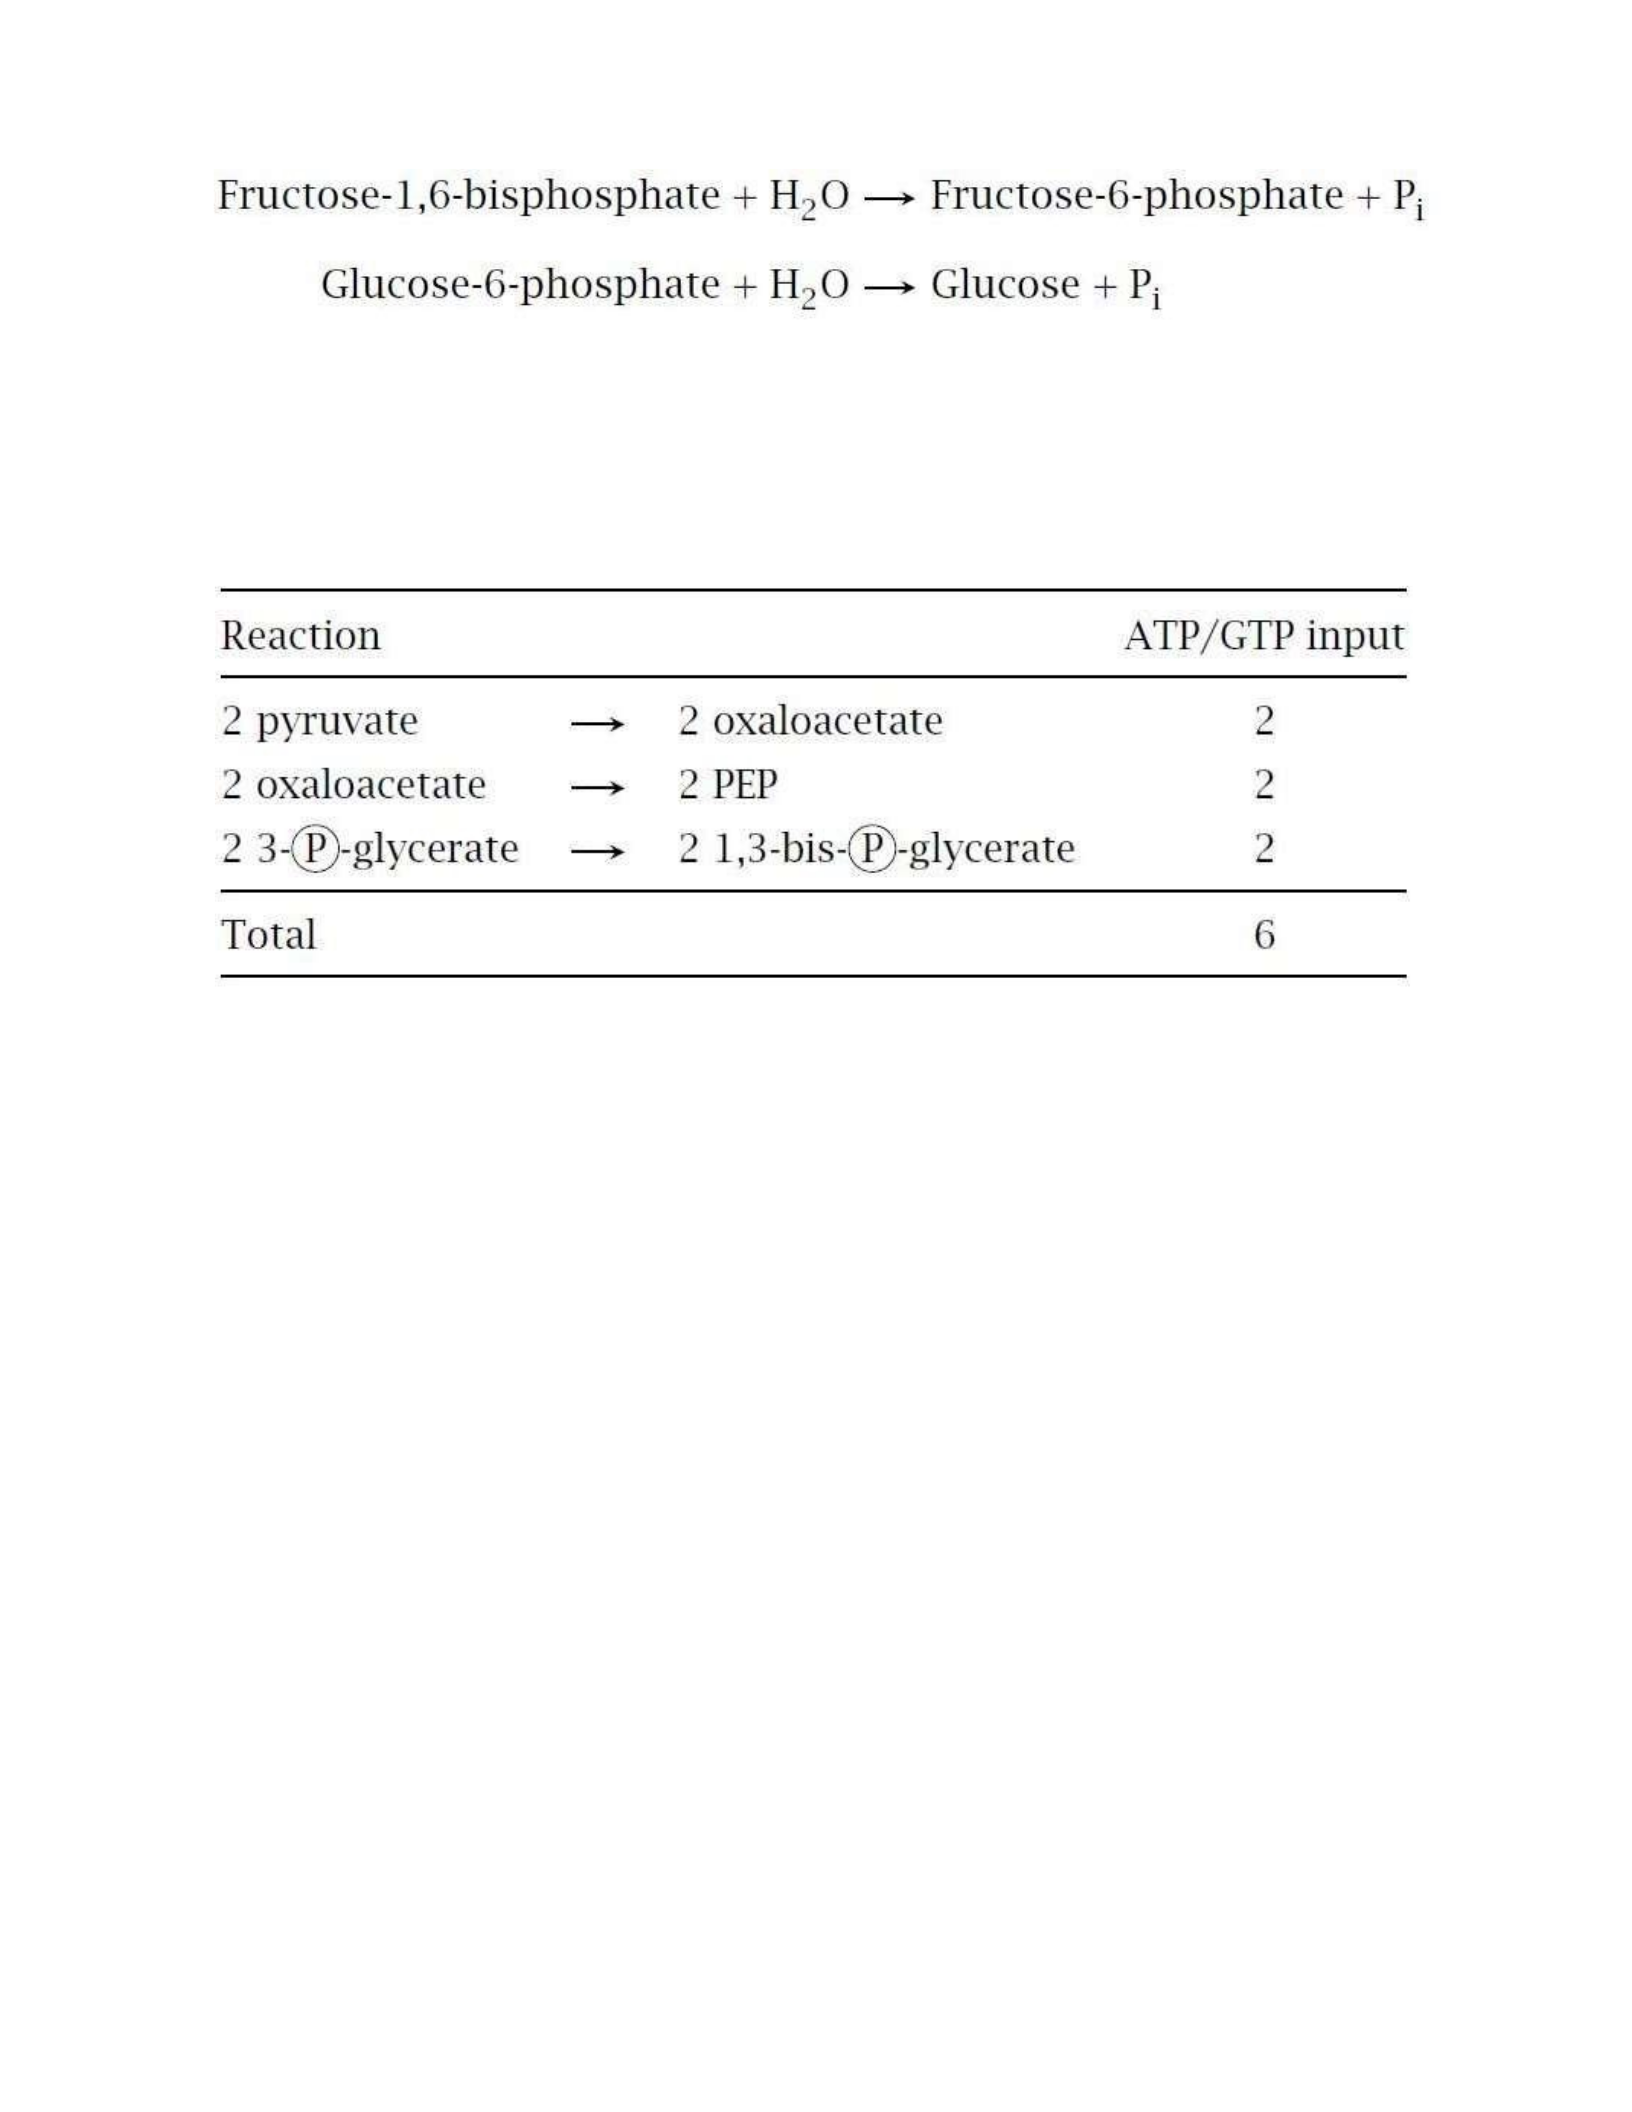
Notes: These reactions revert the substrate phosphorylations that occur in the first and the third step of
glycolysis, which are catalyzed by hexokinase and phosphofructokinase, respectively. The phosphate
groups are simply hydrolyzed off, which is not a very difficult sort of reaction.
Energy balance of gluconeogenesis
Gluconeogenesis requires an input of six equivalents of ATP or GTP for each molecule of glucose. In
glycolysis, there was a net gain of only two molecules of ATP per molecule of glucose. The expenditure
of an extra four molecules of ATP in gluconeogenesis reverts the energy balance of the pathway, so that it
actually proceeds in the opposite direction. Formation of no more than two ATP molecules makes it
exergonic to turn glucose into pyruvate, whereas expenditure of six ATP equivalents makes it exergonic to
turn pyruvate back into glucose.
Interactions of gluconeogenesis with other pathways
As pointed out above, substrate carbon for gluconeogenesis accrues mostly from amino acid degradation
and is harvested at the level of pyruvate or of TCA cycle intermediates. Pyruvate carboxylase, which turns
pyruvate into a TCA cycle intermediate, is important not only in gluconeogenesis but also in the
replenishment of TCA cycle intermediates that may become depleted due to diversion to the biosynthesis
of amino acids or heme. Therefore, this enzyme is expressed not only in the organs that perform
gluconeogenesis (liver and kidneys) but ubiquitously. Gluconeogenesis is also part of two interorgan
cycles, namely the Cori cycle and the glucose-alanine cycle.
Ethanol degradation inhibits gluconeogenesis
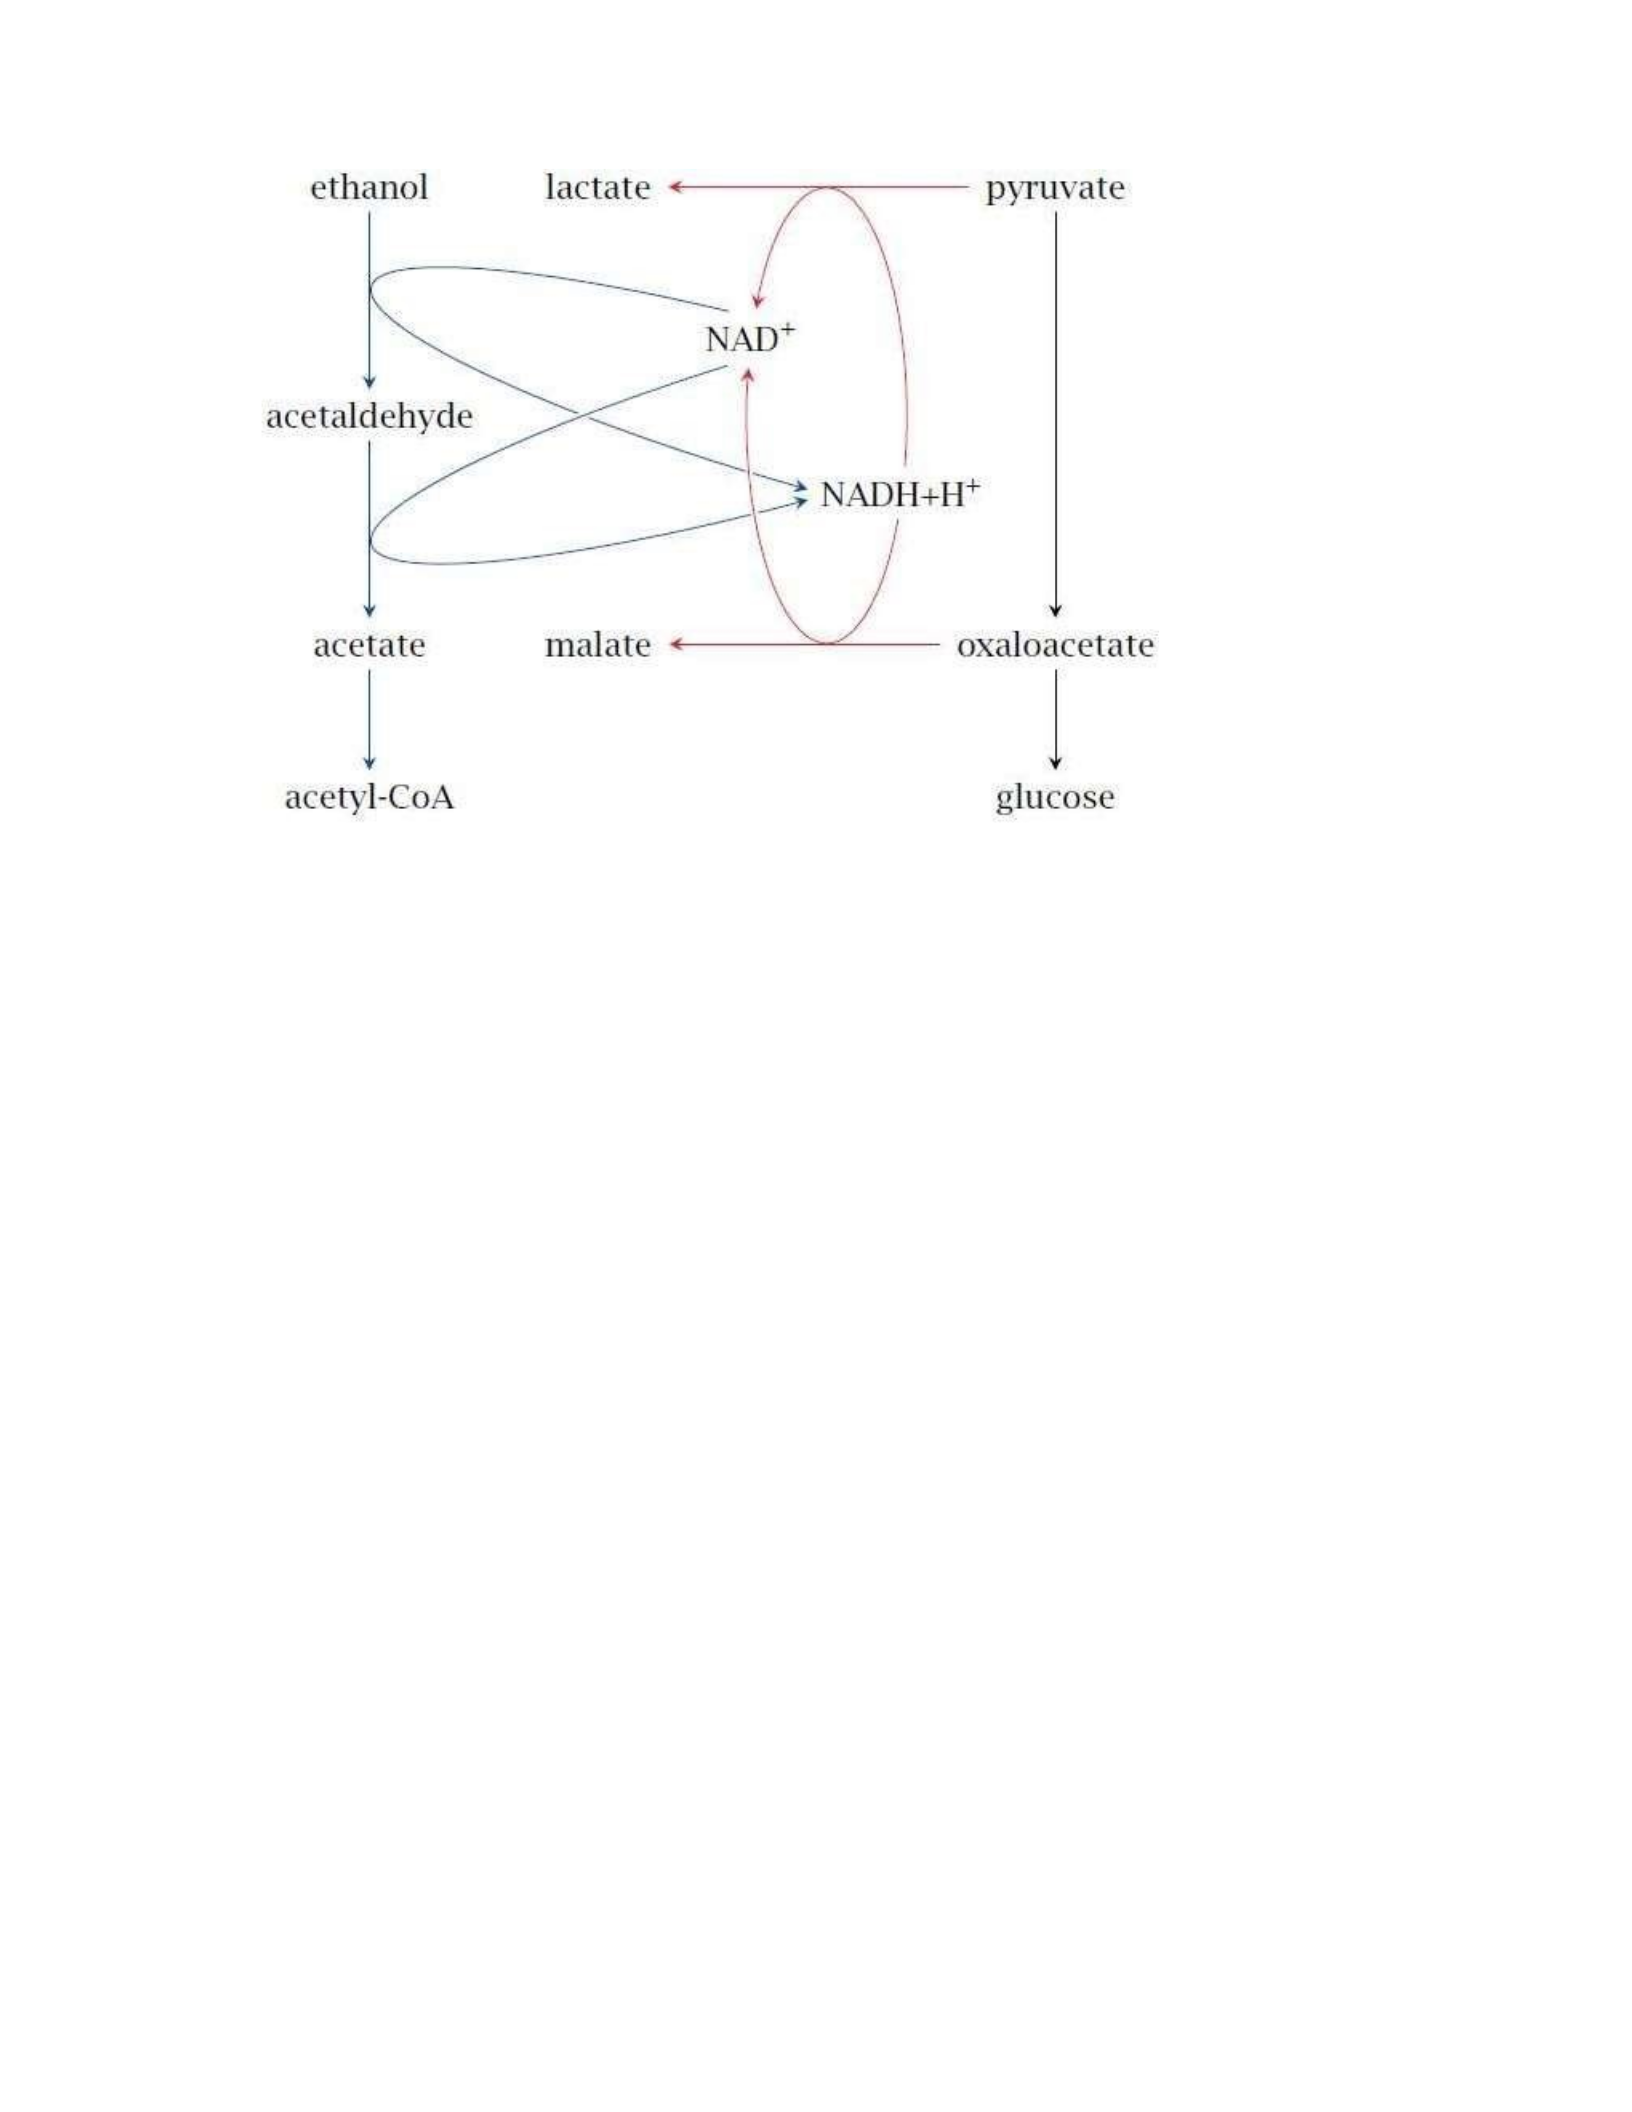
Notes: Like gluconeogenesis, ethanol degradation occurs in the liver. The utilization of one molecule of
ethanol by alcohol dehydrogenase and then aldehyde dehydrogenase reduces two equivalents of NAD+ to
NADH. This raises the cytosolic [NADH]/[NAD+] ratio, which in turn reduces both pyruvate and
oxaloacetate and thus deprives gluconeogenesis of its substrates. In alcoholic patients, this problem is
often compounded by a low intake of carbohydrates. Clinically manifest hypoglycemia with
unconsciousness is a well-known and potentially dangerous complication in alcohol addiction.
PYRUVATE DEHYDROGENASE AND THE CITRIC ACID CYCLE (aerobic fate of pyruvate)
In the complete degradation of pyruvate, pyruvate dehydrogenase (PDH) and the citric acid cycle perform
the oxidation of all substrate carbon to CO2. The hydrogen is retained in reduced form; it is subsequently
oxidized in the respiratory chain.
Pyruvate degradation occurs in the mitochondria
The first step is by Pyruvate dehydrogenase. This enzyme links glycolysis and TCA cycle.
In the mitochondrial matrix, pyruvate is oxidatively decarboxylated by the pyruvate dehydrogenase
complex to form acetyl CoA. This irreversible reaction is the link between glycolysis and the citric
acid cycle.
Note that the pyruvate dehydrogenase complex produces CO2 and captures high-transfer- potential
electrons in the form of NADH. Thus, the pyruvate dehydrogenase reaction has many of the key
features of the reactions of the citric acid cycle itself.
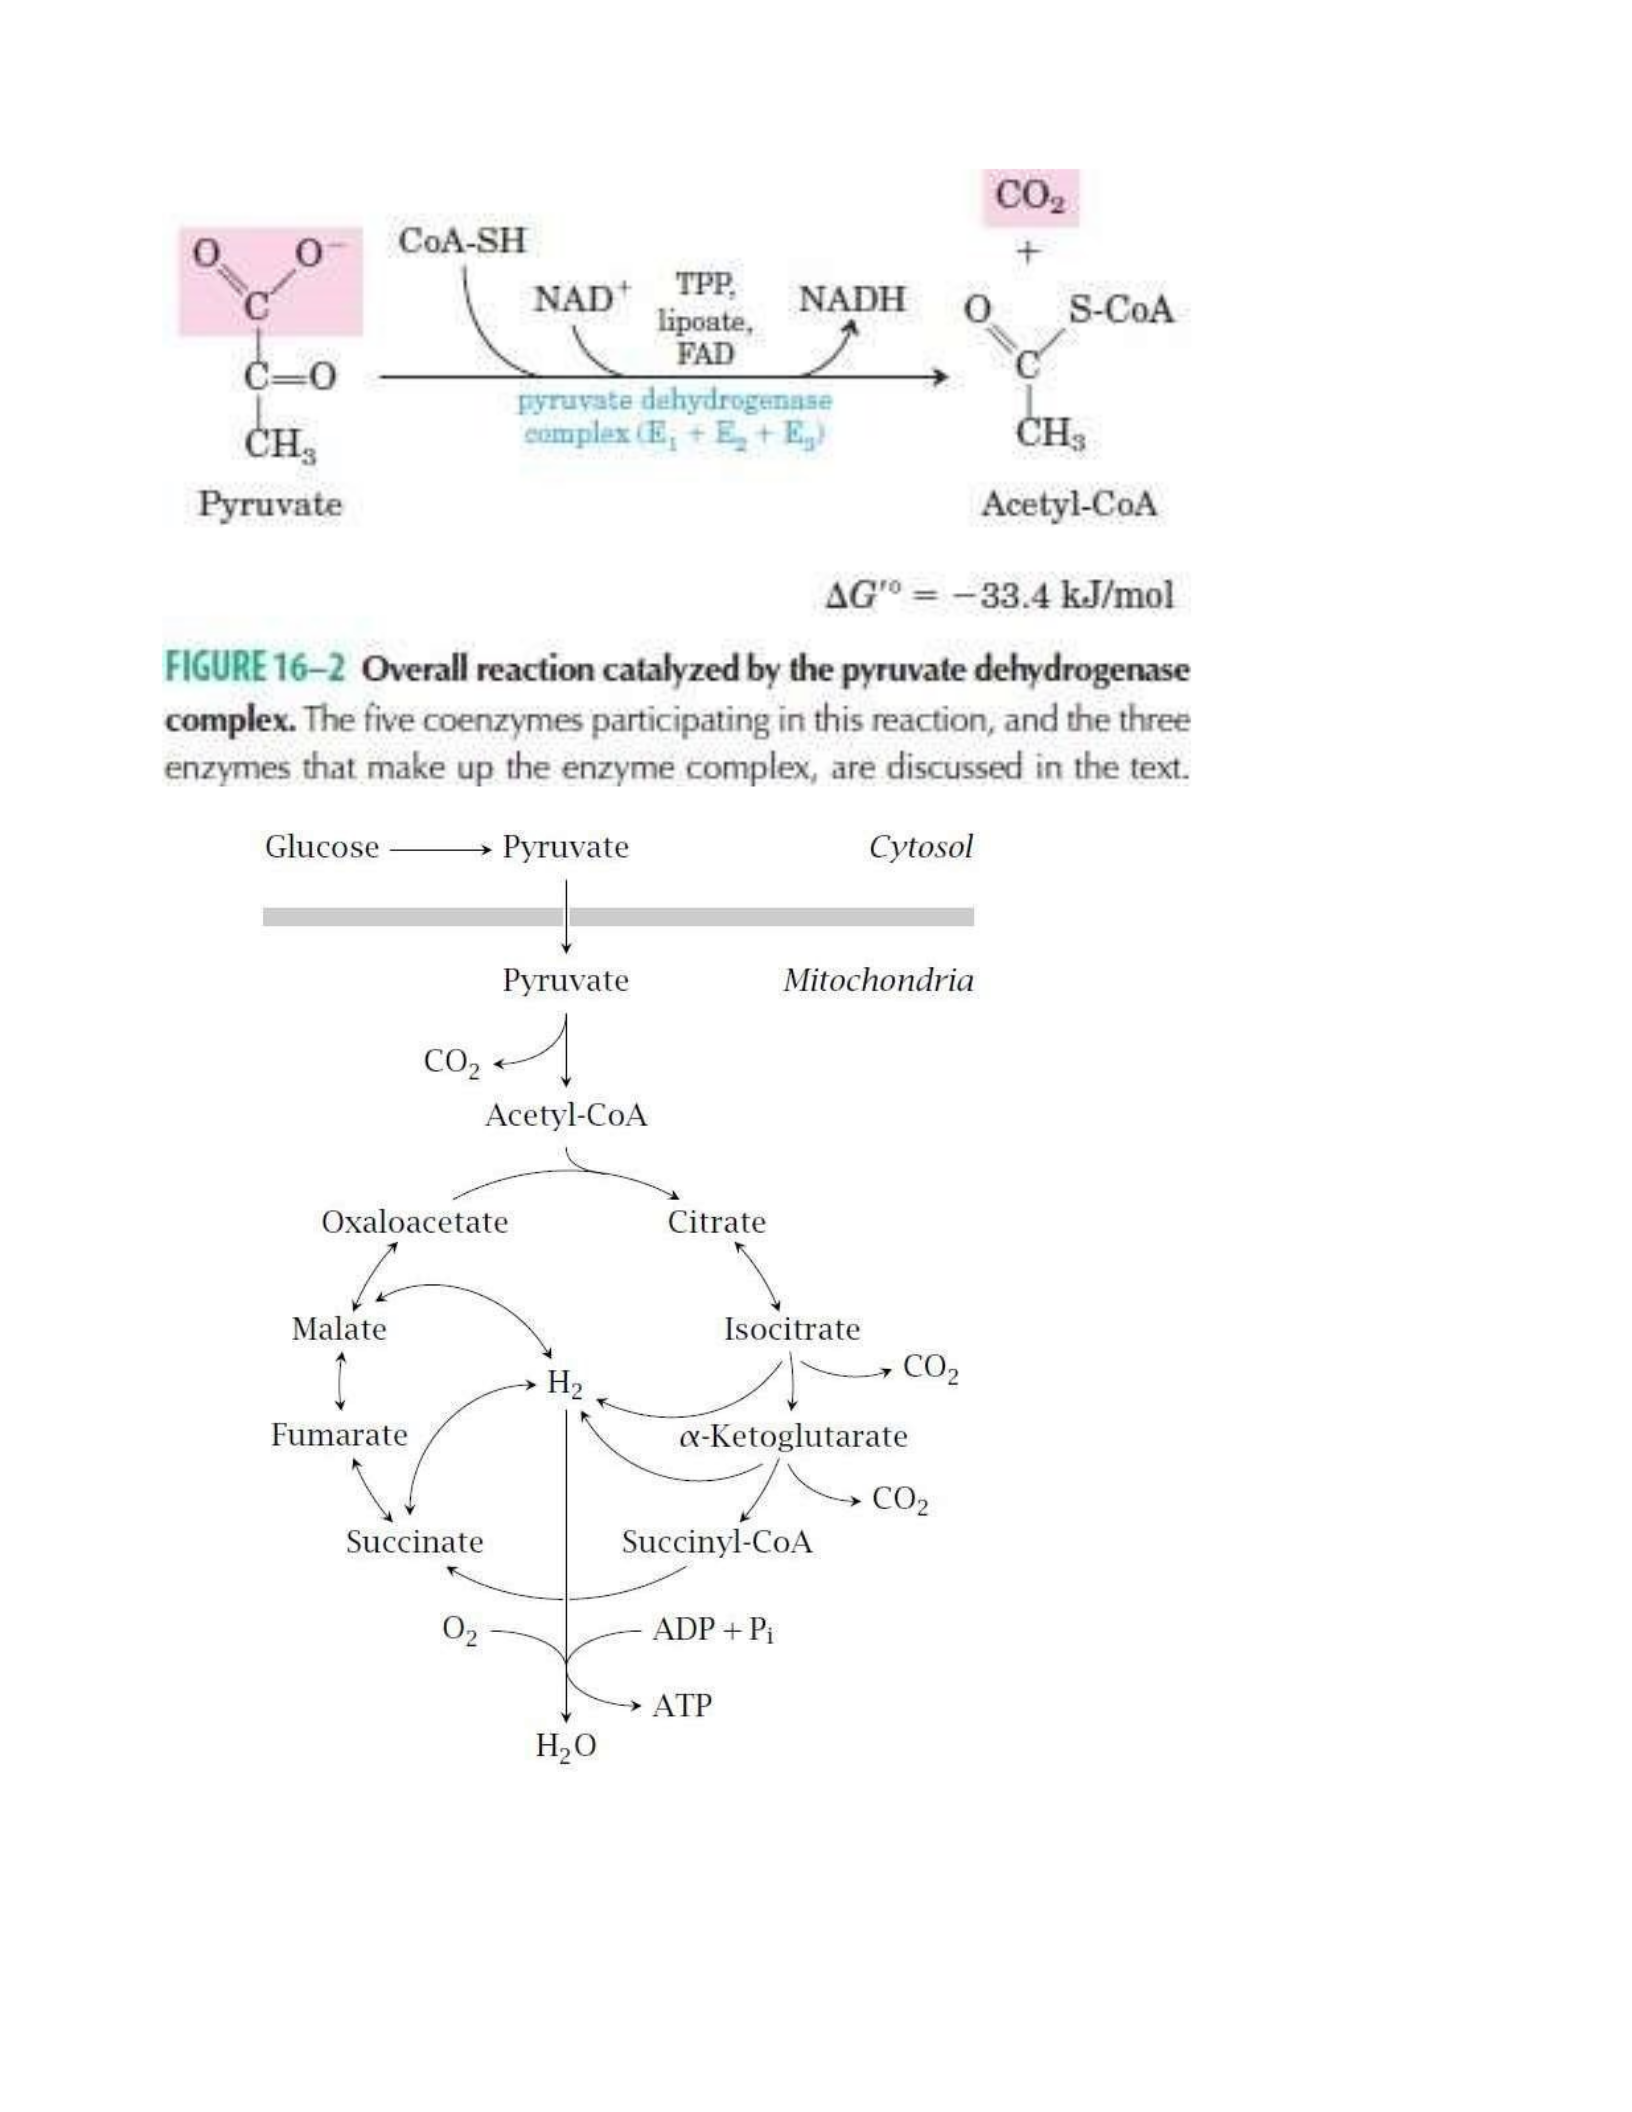
Notes: Pyruvate is produced by glycolysis in the cytosol, while PDH and all subsequent degradative steps are
located in the mitochondria. Therefore, pyruvate needs to be transported from the cytosol to the
mitochondrial matrix. The outer mitochondrial membrane contains porins, which are membrane proteins that
form non-specific pores and allow free permeation of most small metabolites, including pyruvate. In contrast,
the inner mitochondrial membrane is much more restrictive, and it is permeable to only those metabolites for

which it contains specific carrier systems. The pyruvate carrier is an active transporter that exchanges
cytosolic pyruvate for mitochondrial hydroxide (OH–). Red blood cells and blood platelets lack mitochondria
and accordingly cannot degrade pyruvate. These cells reduce pyruvate to lactate, which they then release into
the bloodstream.
The citric acid cycle
Oxidative degradation of all foodstuffs—carbohydrates, amino acids, and fat—proceeds via acetyl-CoA,
which therefore is a central hub of energy metabolism. The next step toward complete oxidation is the
citric acid cycle, also referred to as the Krebs cycle or the tricarboxylic acid cycle (TCA cycle for short).
While the substrate carbon enters the TCA cycle as acetyl-CoA, the coenzyme A moiety is simply
hydrolyzed off in the very first reaction; therefore, with only a little sleight of hand, we can neglect
coenzyme A and substitute acetate for acetyl-CoA as the substrate. The basic idea of the TCA cycle
consists in releasing the substrate carbon as CO2, while retaining the substrate hydrogen for “cold
combustion” in the respiratory chain.
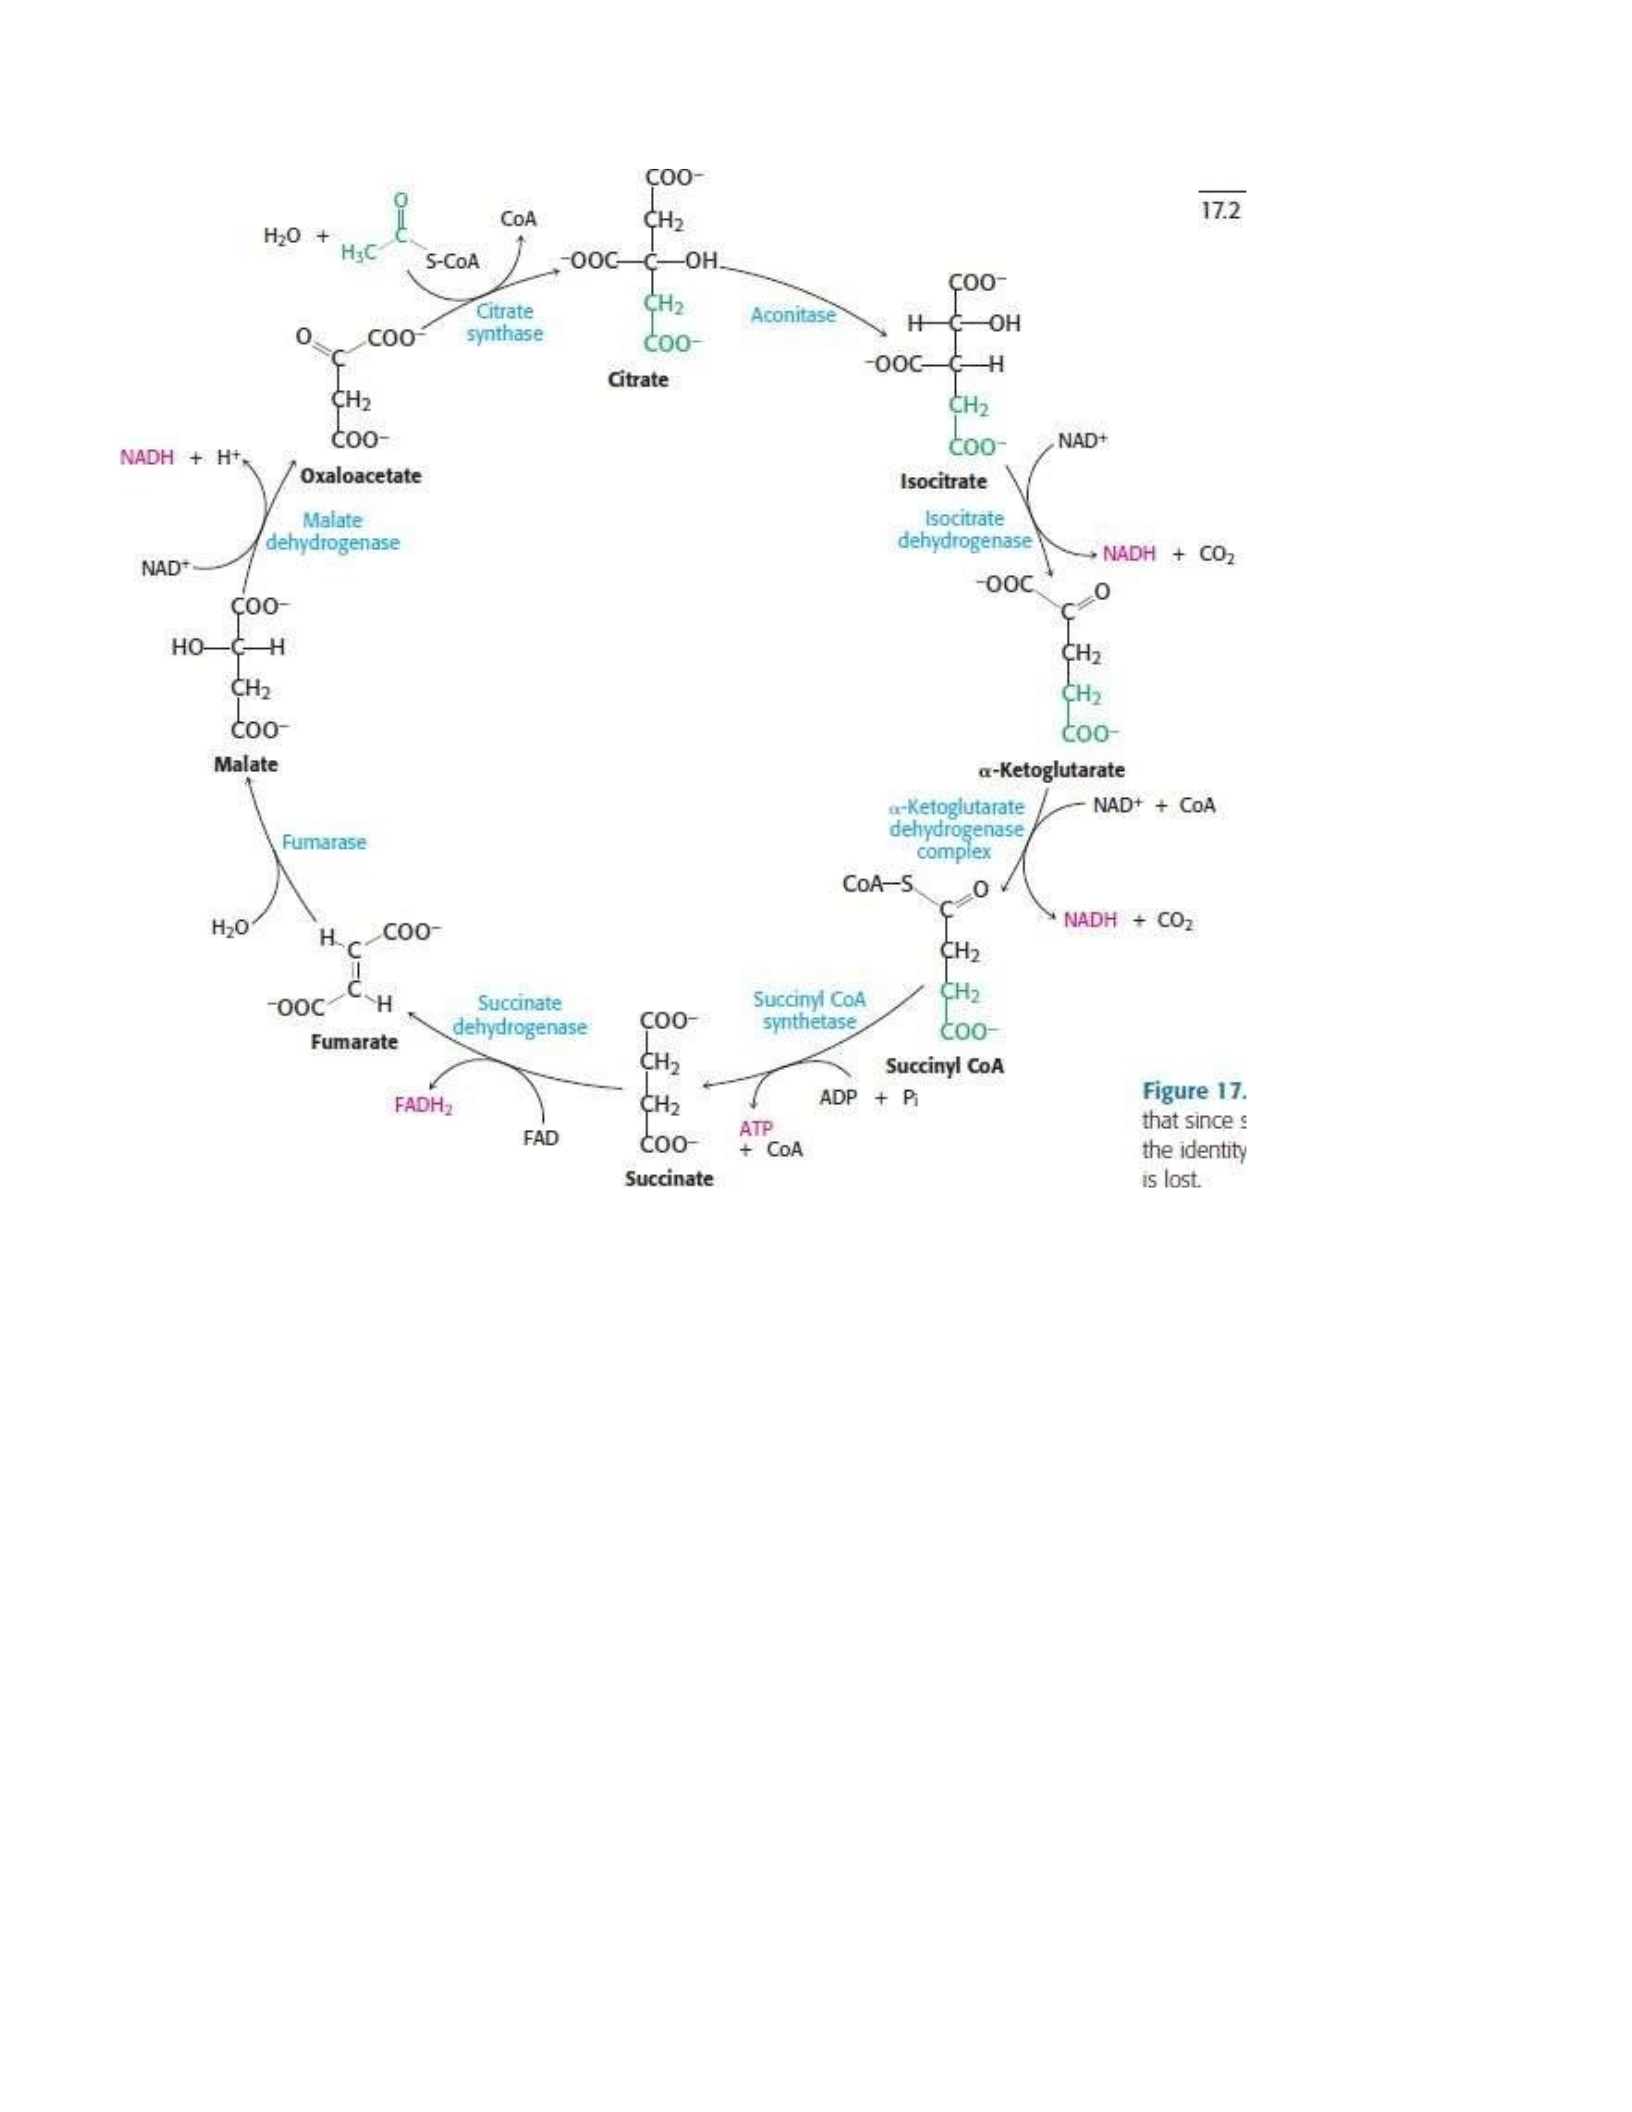
Notes: The paragraph numbers below correspond to those of the reactions in the figure. The first reaction in
the figure is the second in the cycle overall, which is why it gets the number 2.
2. The hydroxyl group in the newly formed citrate is shifted to an adjacent carbon to yield isocitrate. This
reaction is catalyzed by citrate isomerase and involves the transient elimination of water across the two
carbons involved; the water is then added back in the reverse orientation.
3. Isocitrate is decarboxylated and dehydrogenated by isocitrate dehydrogenase, which yields α-
ketoglutarate. In contrast to the pyruvate dehydrogenase reaction, dehydrogenation precedes
decarboxylation. The dehydrogenated intermediate is known as oxalosuccinate.
4. α-Ketoglutarate is converted to succinyl-CoA by α-ketoglutarate dehydrogenase. This catalytic
mechanism of this enzyme is completely analogous to that of pyruvate dehydrogenase.
5. Succinyl-CoA is converted to succinate by succinate thiokinase, and GDP is concomitantly
phosphorylated to GTP
6. Succinate is dehydrogenated across the CH2−CH2 bond by succinate dehydrogenaseto yield fumarate.
The coenzyme used in this reaction is flavin adenine dinucleotide (FAD). As a rule of thumb, you can
assume that FAD is used in the dehydrogenation of CH−CH bonds, whereas either NAD+ or NADP+
are used in the dehydrogenation of CH−OH bonds. While all other enzymes in the TCA are in aqueous
solution in theinner mitochondrial membrane; it is identical with complex II of the respiratory chain.
7. Fumarate is hydrated to l-malate by fumarase.
8. Malate is dehydrogenated by malate dehydrogenase to oxaloacetate. This step regenerates oxaloacetate,
which can again enter the citrate synthase reaction, and thus completes the cycle.
How is oxaloacetate replenished? Mammals lack the enzymes for the net conversion of acetyl
CoA into oxaloacetate or any other citric acid cycle intermediate. Rather, oxaloacetate is formed by
the carboxylation of pyruvate, in a reaction catalyzed by the biotin-dependent enzyme pyruvate
carboxylase
Recall that this enzyme plays a crucial role in gluconeogenesis. It is active only in the presence of
acetyl CoA, which signifies the need for more oxaloacetate. If the energy charge is high,
oxaloacetate is converted into glucose. If the energy charge is low, oxaloacetate replenishes the
citric acid cycle. The synthesis of oxaloacetate by the carboxylation of pyruvate is an example of an
anaplerotic reactions (reactions which replenish the TCA cycle)
THE RESPIRATORY CHAIN
Introduction
In the respiratory chain, the NADH and FADH2 that was accumulated in the preceding degradative
pathways is finally disposed of by reacting it with molecular oxygen. The free energy of this “cold
combustion” is used to generate ATP. The amount of ATP generated in the respiratory chain far exceeds the

modest quantities produced in the upstream pathways; this is the reason why only aerobic metabolism
enables us to sustain physical exertion for extended periods of time.
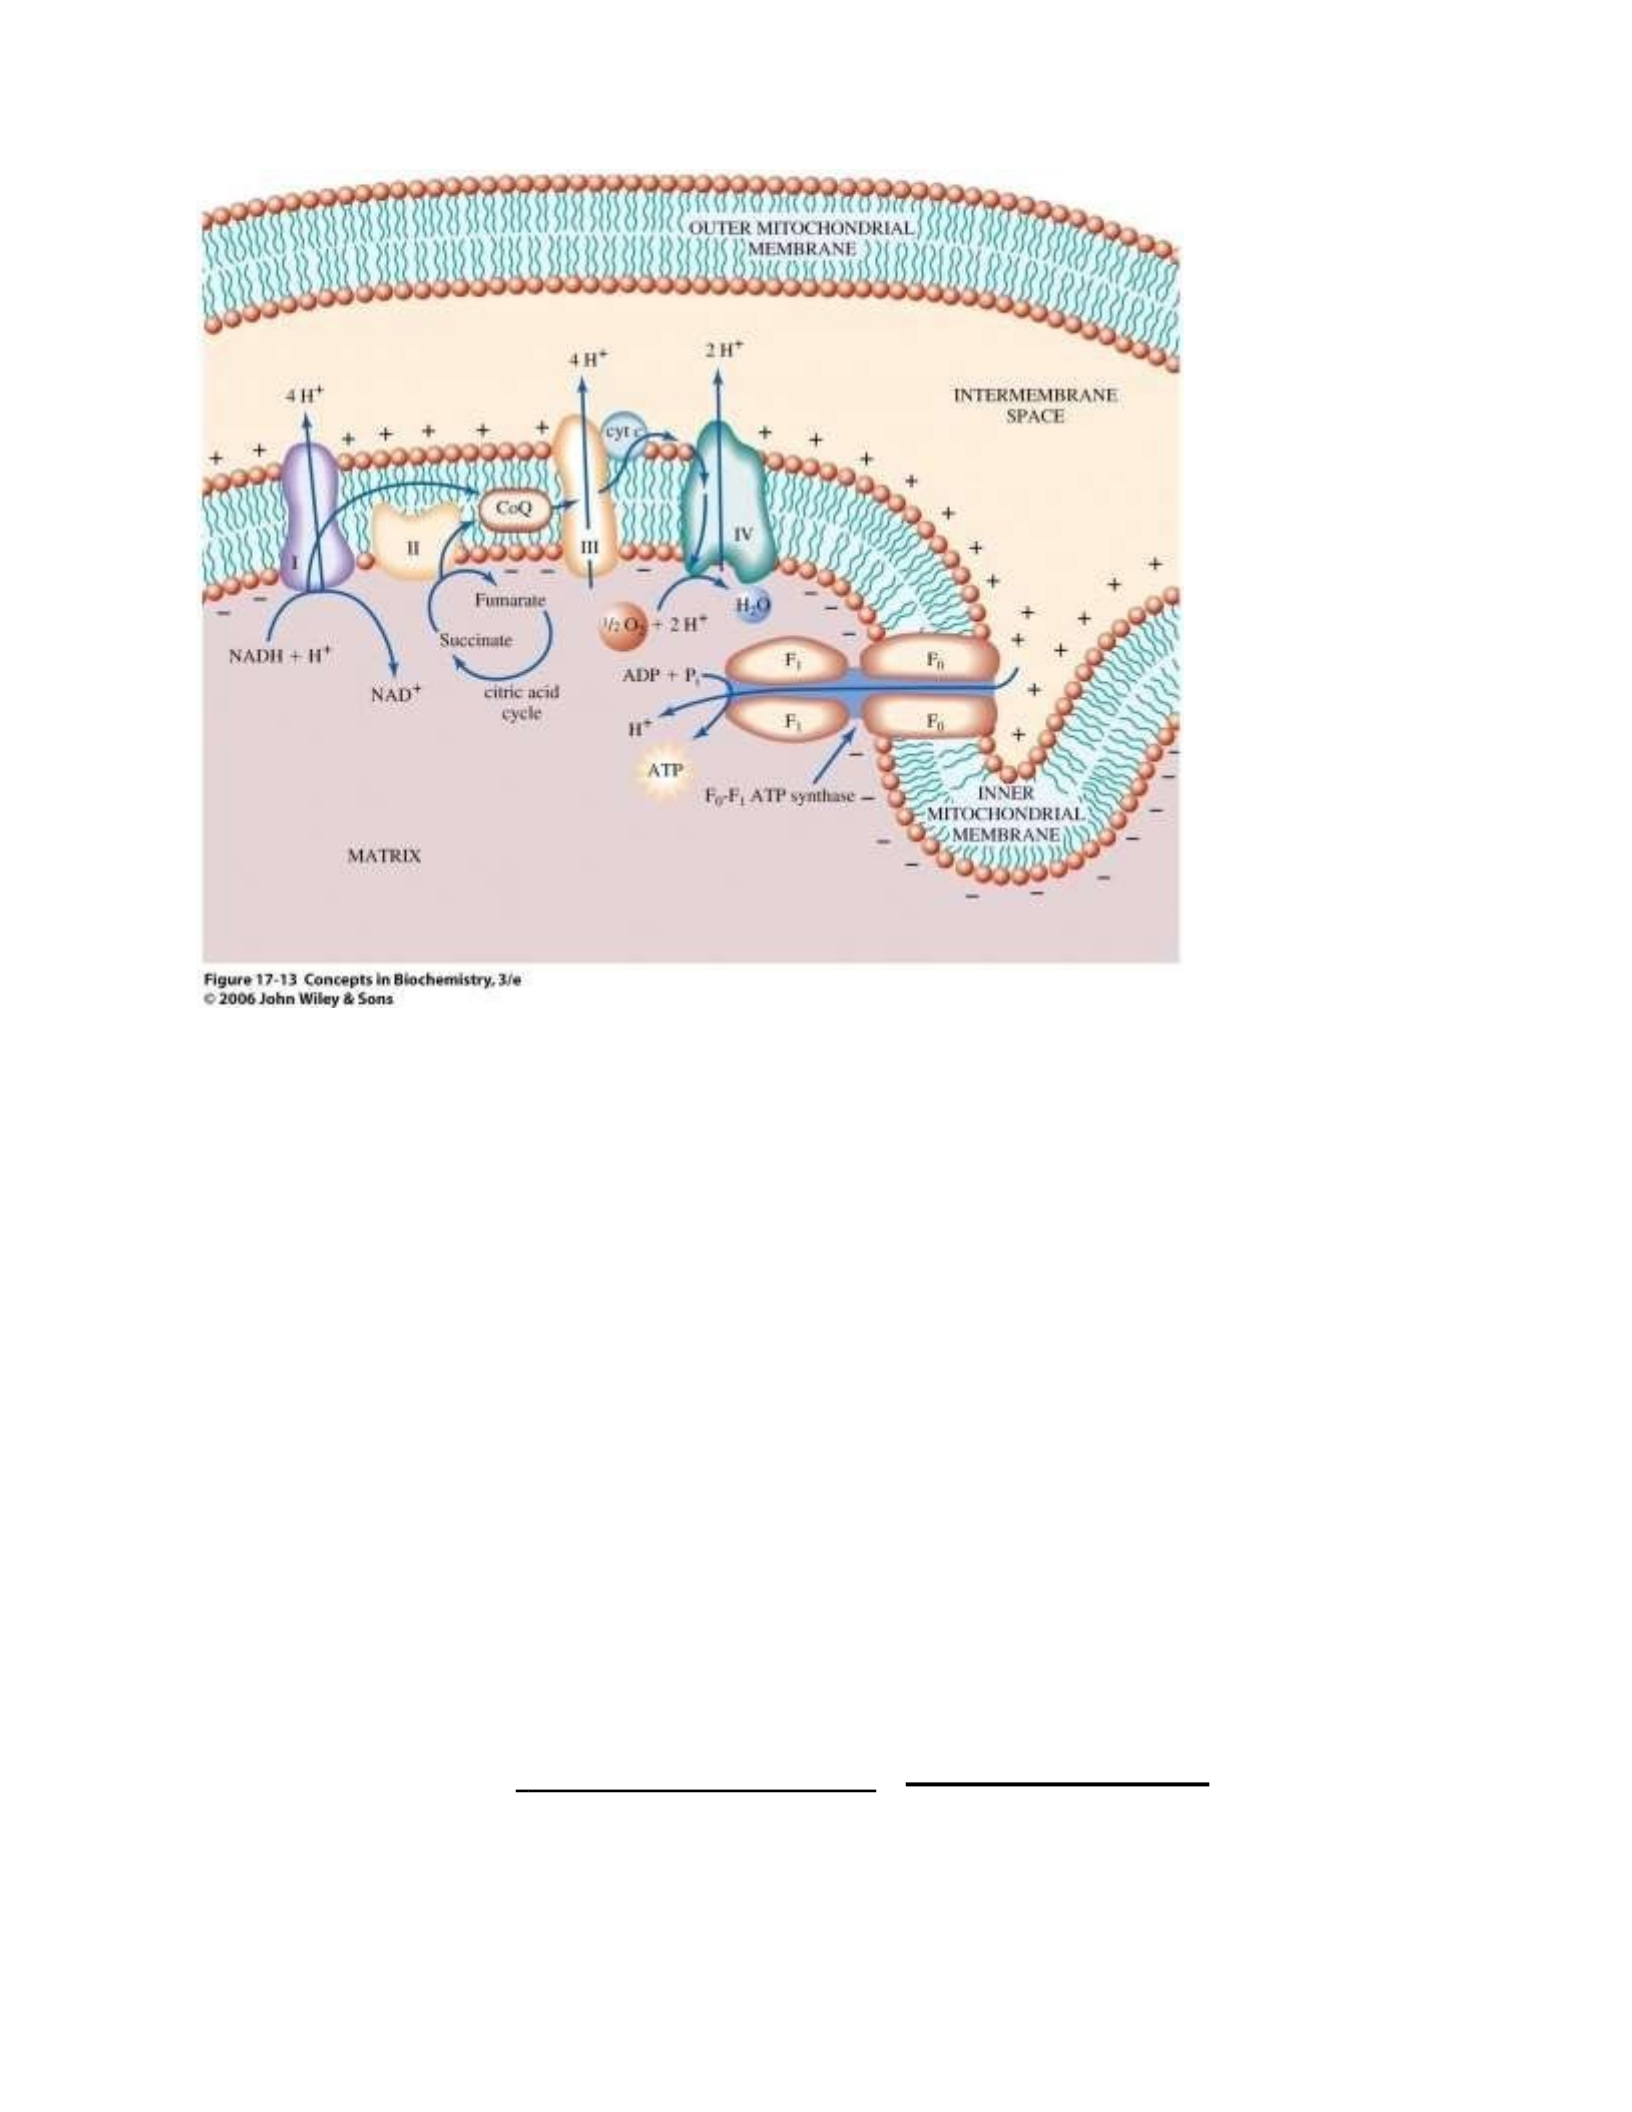
Electron Transport Chain is the process by which NADH and FADH2 are oxidized and a proton gradient is
formed while Oxidative phosphorylation is the process of making ATP by using the proton gradient
generated by the ETC. This two processes are coupled together.
The workings of the respiratory chain are quite different from all other pathways in human metabolism.
Those other pathways consist of a succession of discrete enzymatic reactions. In as much as they
contribute to the production ATP, the energy is always passed from one energy-rich bond to the next, with
a newly created phosphoanhydride bond in ATP as the final recipient. In contrast, the respiratory chain
combines chemical reactions with physical forces that are not pinned down to individual molecules, and
the energy is stored and converted in novel ways.
The processes occurs in the inner mitochondrial membrane where the electron transport chain oxidizes reduced
coenzymes while the ATP synthase synthesizes ATP.
(1) Respiratory electron-transport chain (ETC) Series of enzyme complexes embedded in the inner
mitochondrial membrane, which oxidize NADH and FADH2. Oxidation energy is used to transport
protons creating a proton gradient – protons pumped from matrix to intermembrane space across IMM
(2) ATP synthase uses the proton gradient energy to produce ATP; It is the release of the energy in the
gradient back through the membrane through the protein ATP Synthase that drives ATP synthesis
THE ELECTRON TRANSPORT CHAIN
It involves four complexes (I-IV) in the inner mitochondrial membrane.
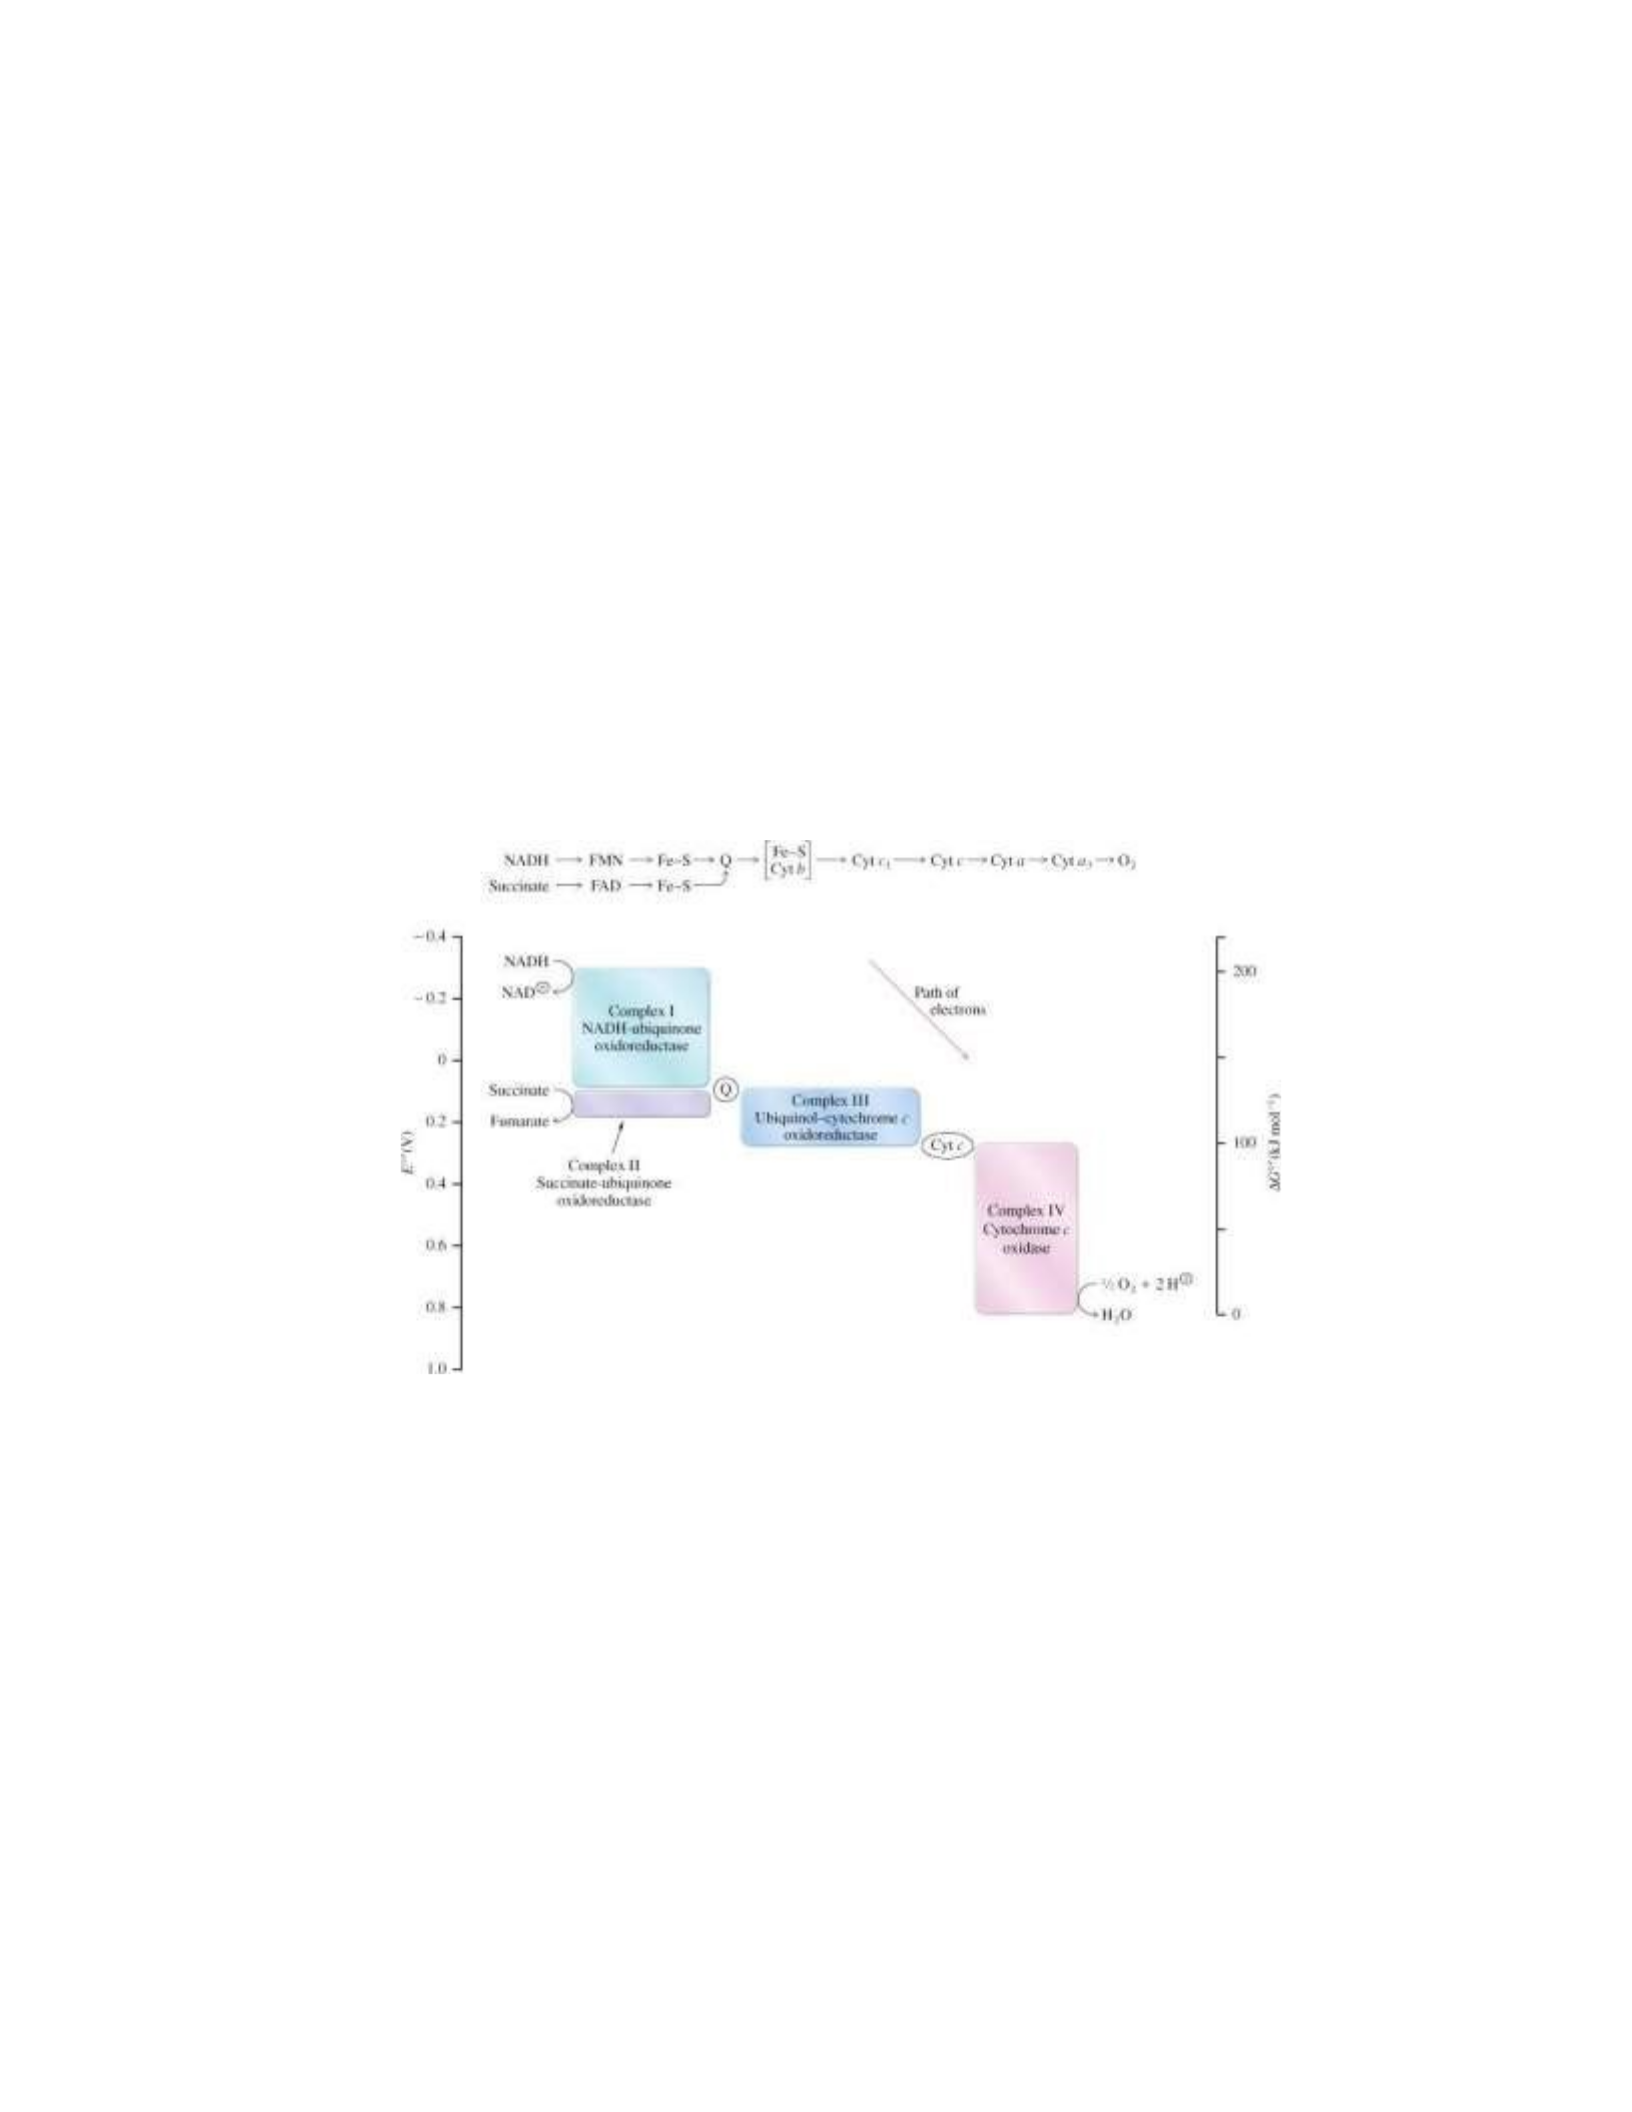
The flow of electrons is spontaneous and thermodynamically favorable because the next carrier has greater
affinity for electrons than the previous
In each reaction, an electron donor is oxidized and an electron acceptor is reduced
–Areduced + Boxidized Aoxidized + Breduced
Compounds differ from one another in how readily they will be oxidized or reduced
–can be compared using Eo’ (volts)
–starting with 1 M “A” and 1 M “B”, the component with most positive (low) redox potential
will be reduced and the component with the most negative (high) reduction potential will be
oxidized
–Electrons flow downhill – spontaneously moving from molecules that are strong electron
DONORS to strong electron ACCEPTORS = move from high energy state to low energy state
–
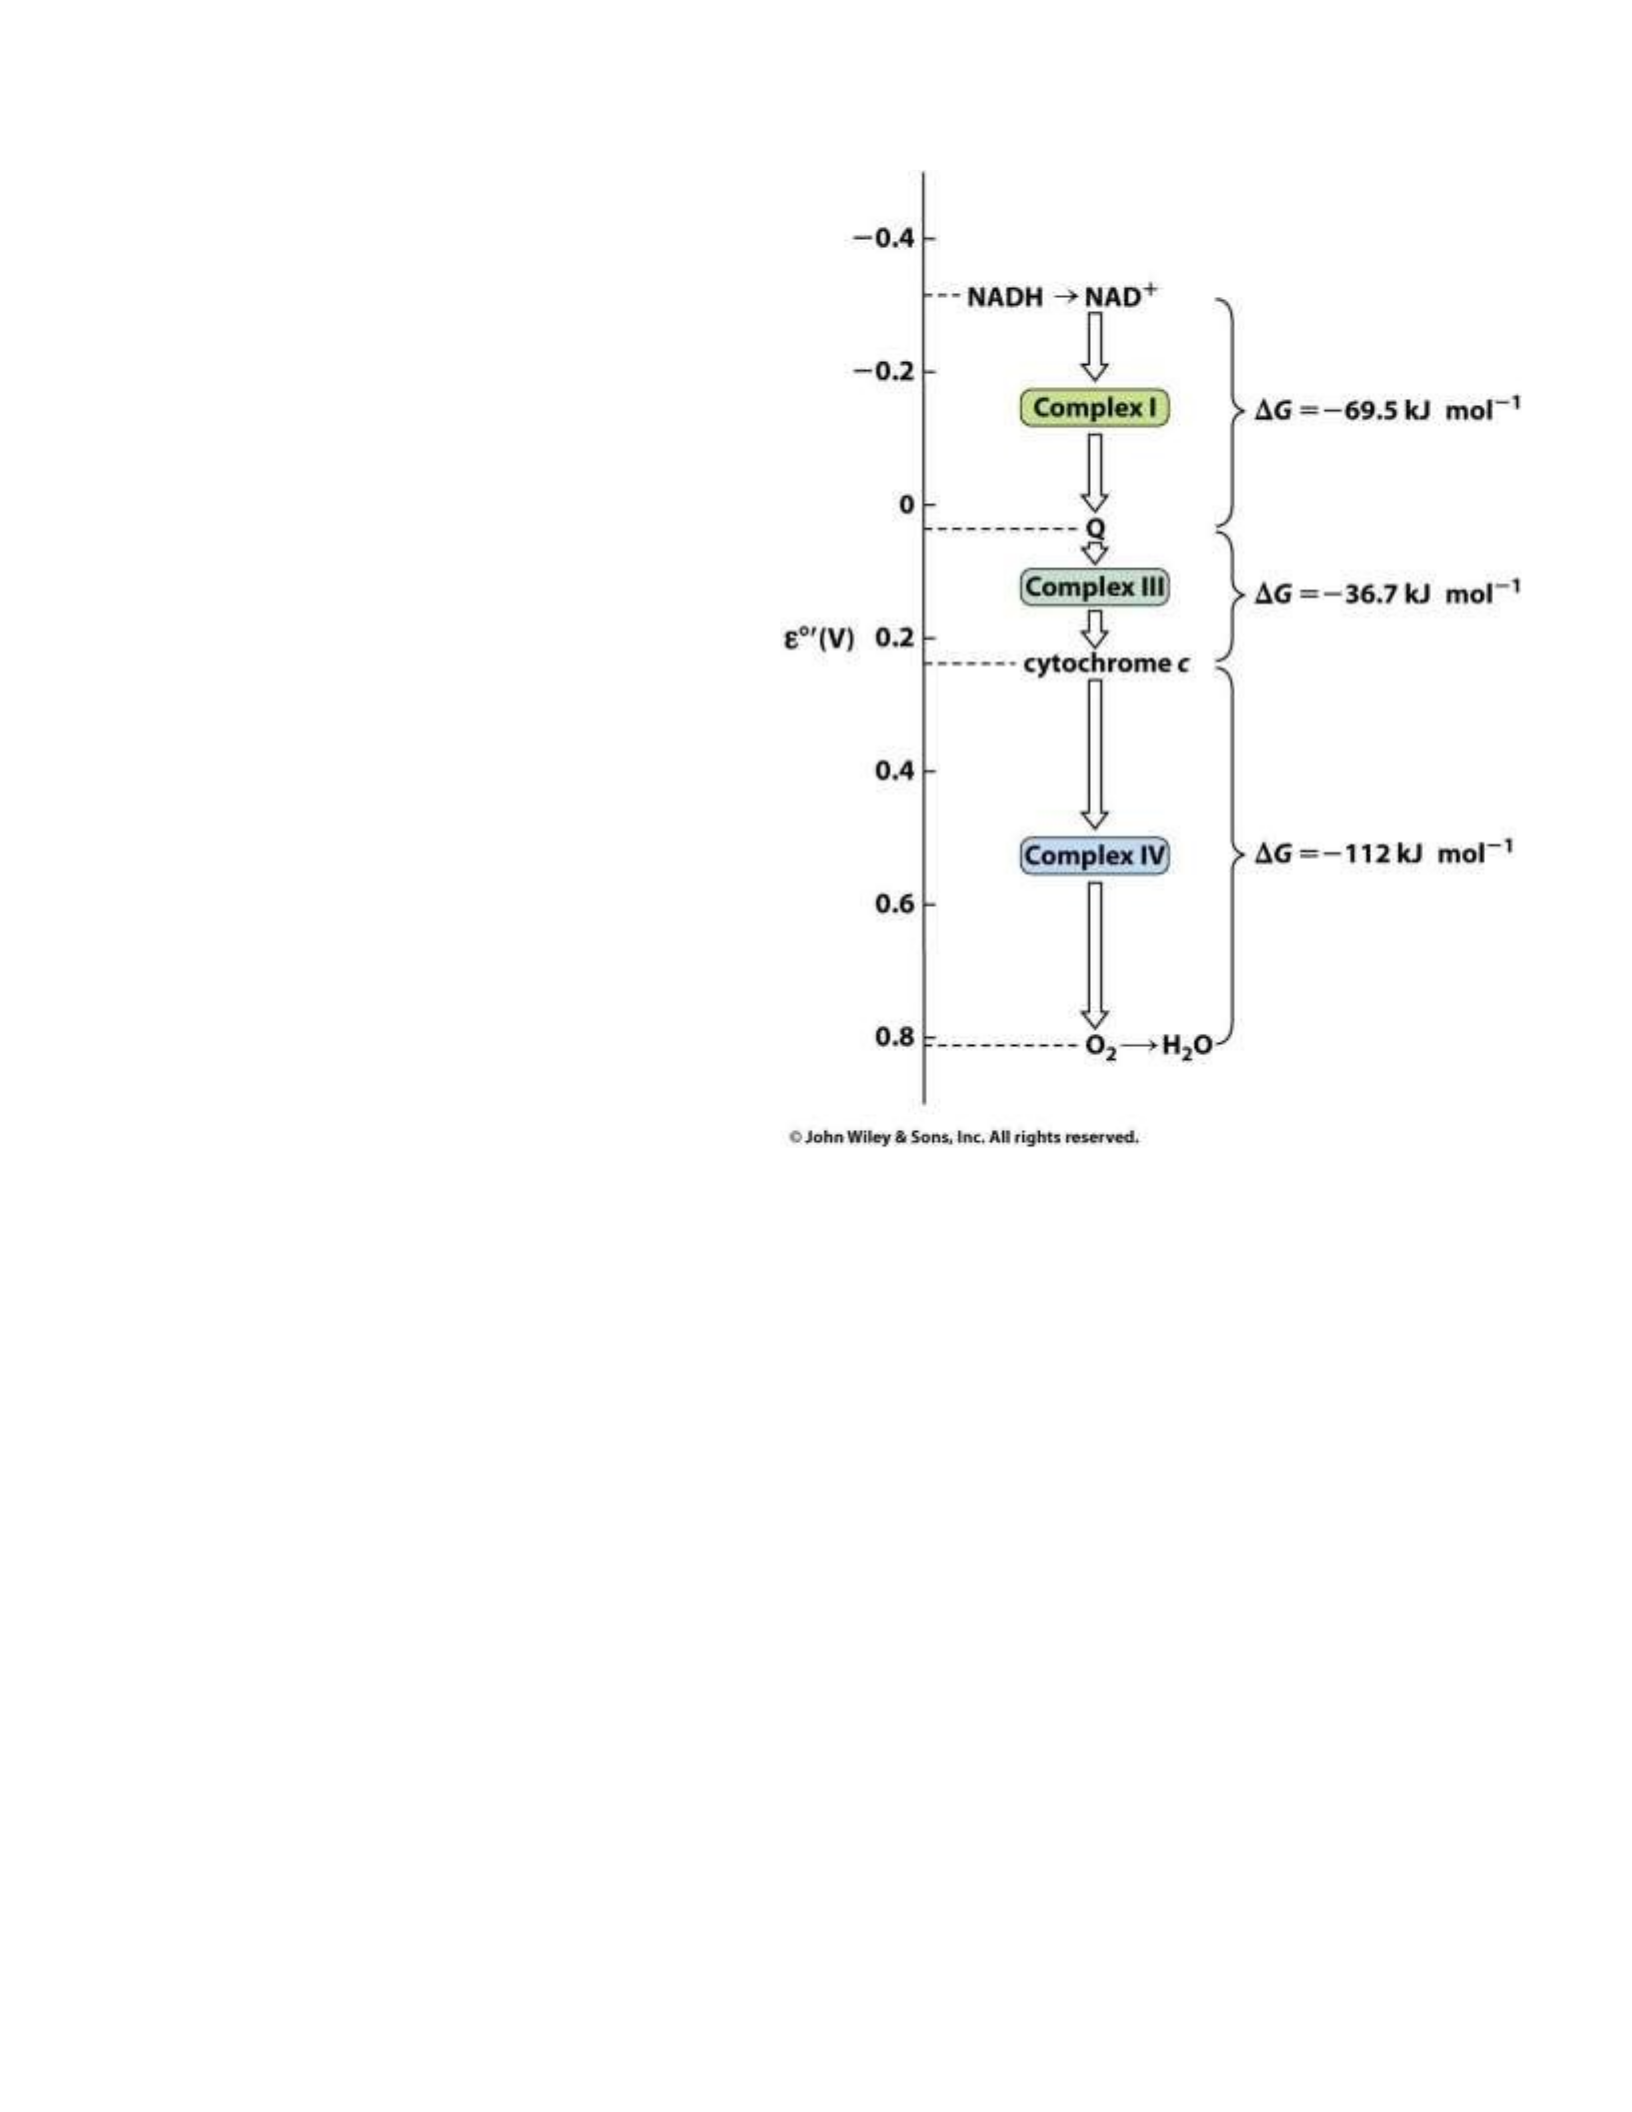
• NADH = strongest donor
• O2 = strongest acceptor
• The redox potential energy of
NADH is released stepwise
via the electron transport chain
– The flow of electrons results in
energy that is released in increments
through the ETC
– Energy is used to pump protons (H+)
across the inner mitochondrial
membrane (IMM) and set up the pH
gradient
– It is the release of the energy in the
gradient back through the membrane
through the intergral membrane
protein
ATP Synthase that drives
ATP synthesis
Note: Electrons from NADH enters at complex I while those from FADH2 enters at complex II.
Co factors in the electron transport chain
Protein components use metal- containing prosthetic groups or flavins to carry electrons. Metal-
containg groups such as iron-sulfur clusters, copper ions and hemes are also used as cofactors In
addition, flavins such as FMN and FAD are also utilized.
Mobile electron carriers serve as links between the ETC complexes. These include ubiquinone
(coenzyme Q) and cytochrome C.
Ubiquinone is a membrane-soluble low molecular weight compound with a long hydrophobic tail
that keeps Q anchored in the mitochondrial inner membrane. Q is a lipid soluble molecule that
diffuses within the lipid bilayer, and shuttles electrons from Complexes I and II and pass them to
III
Cytochrome C is a peripheral membrane protein associated with the outer face of the membrane
and it shuttles electrons from III to IV. Cytochromes are basically heme-containing proteins
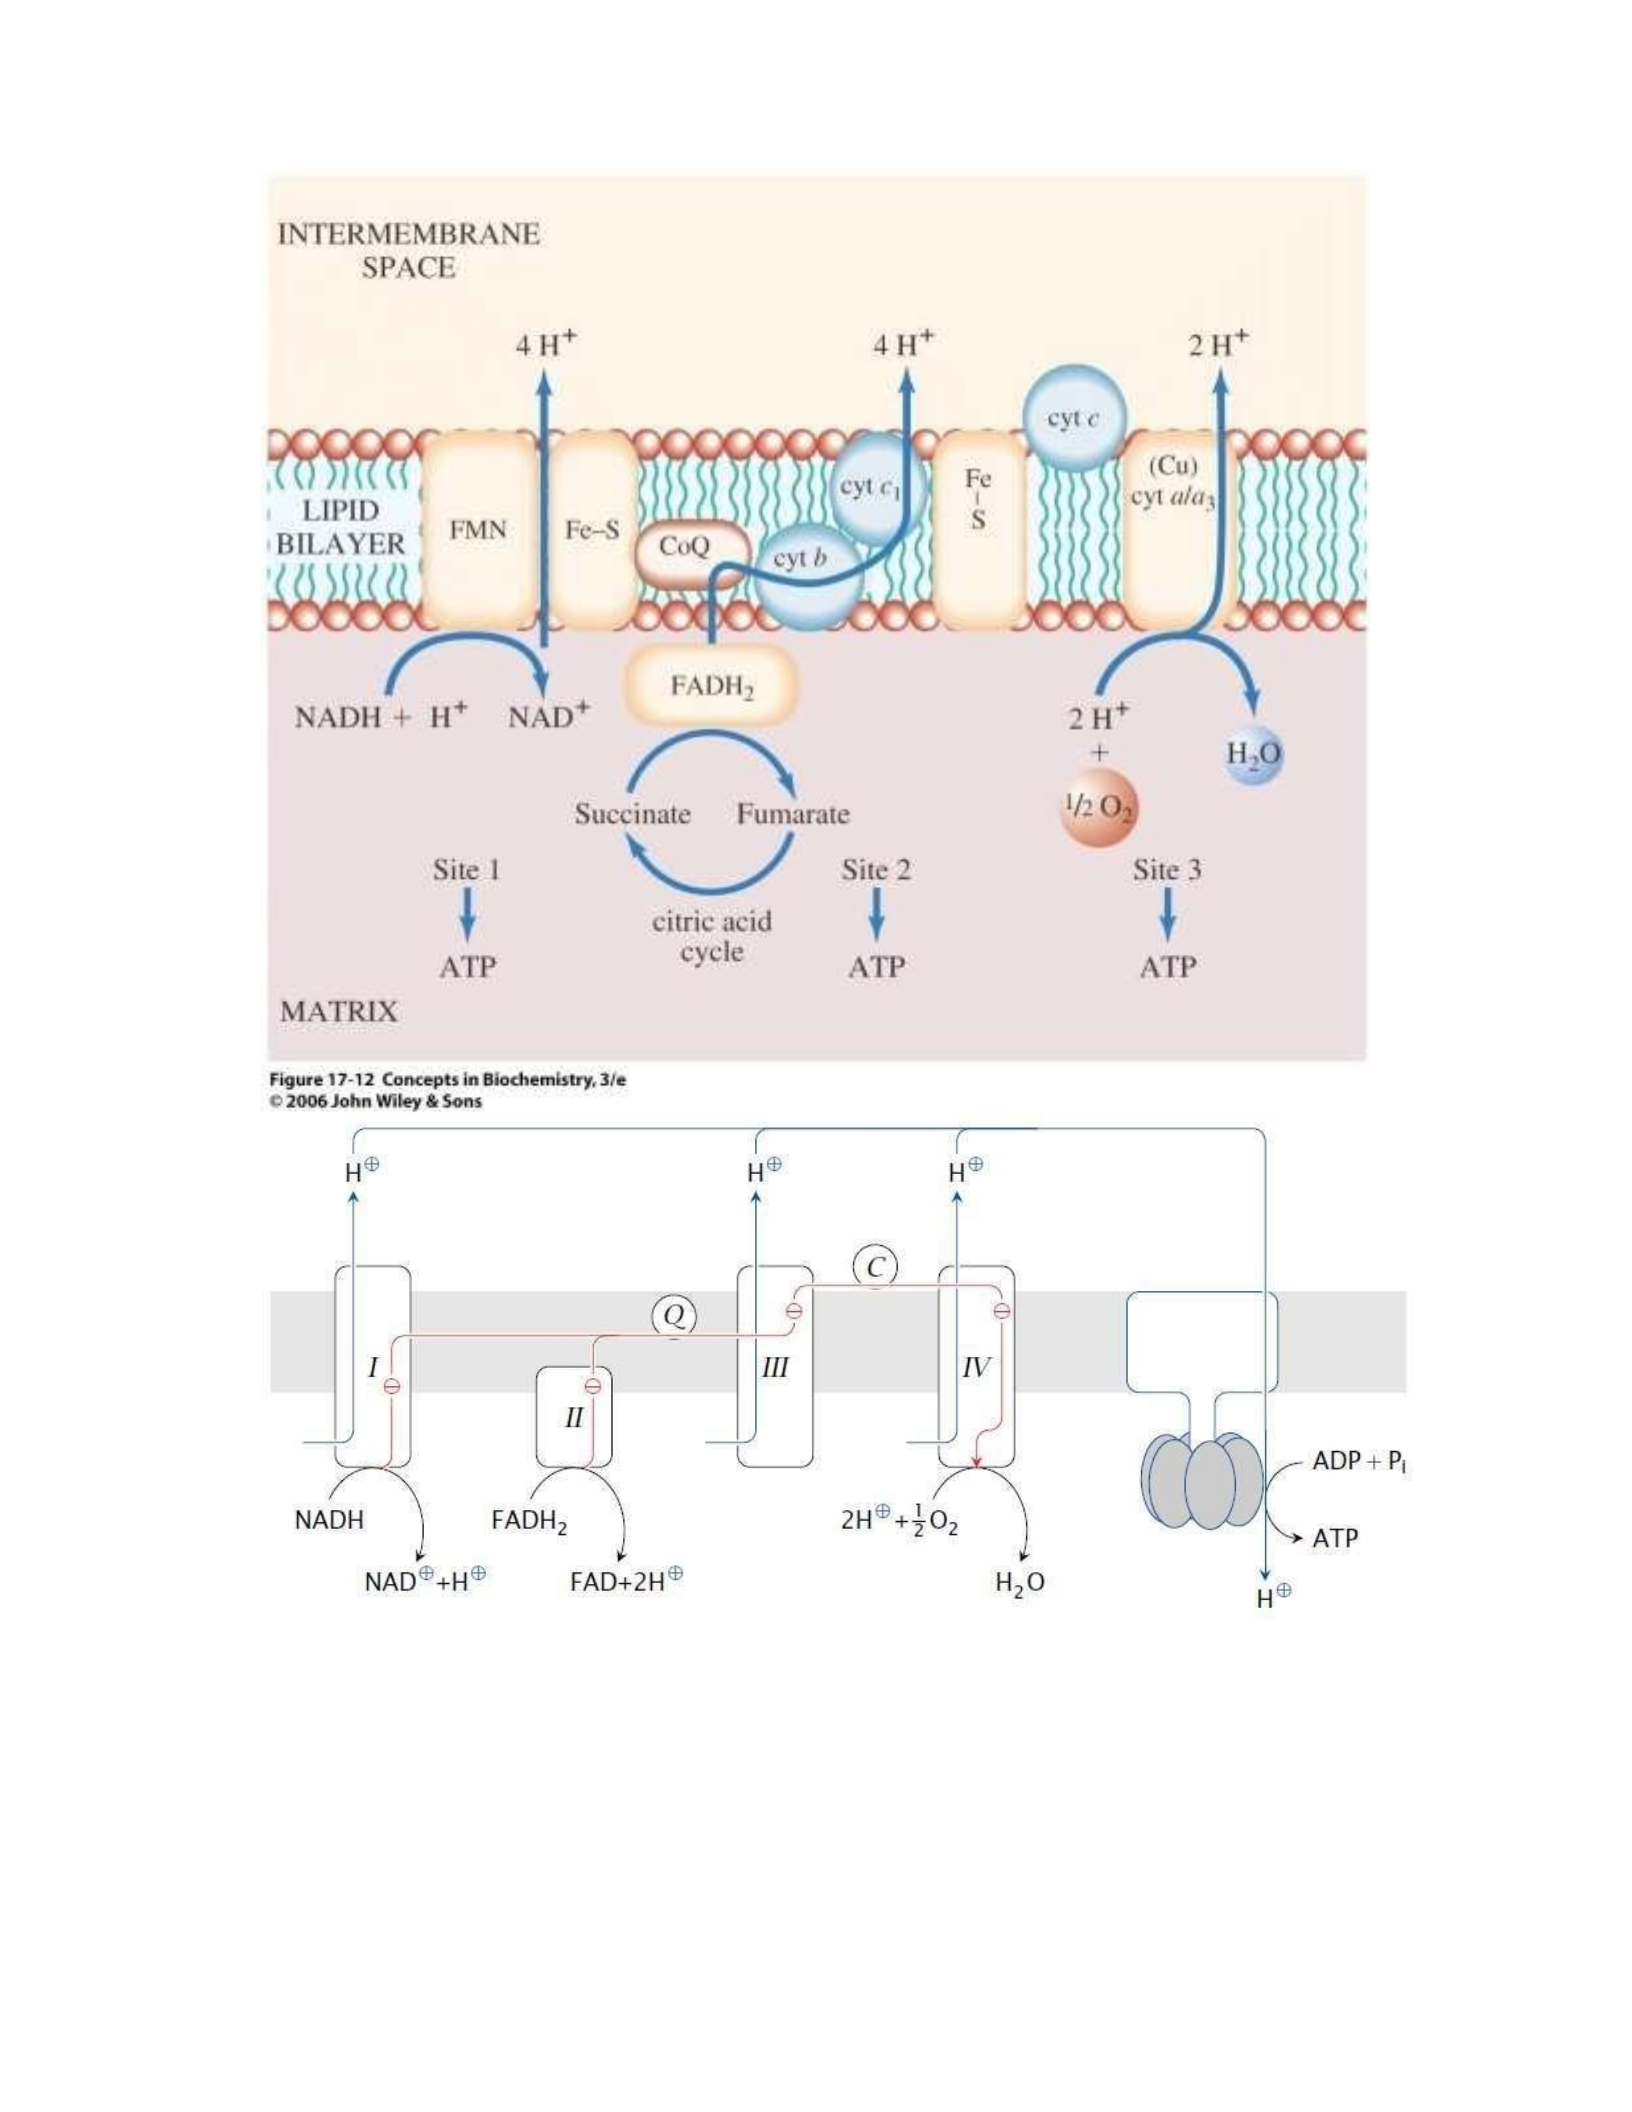
Functional stages in the respiratory chain
1. H2 is abstracted from NADH+H+ and from FADH2
2. The electrons obtained with the hydrogen are passed down a cascade of carrier molecules
located in complexes I–IV, then transferred to O2
3. Powered by electron transport, complexes I, III, and IV expel protons across the inner
mitochondrial membrane

4. The expelled protons reenter the mitochondrion through ATP synthase, driving ATP synthesis
Notes: The electron transport chain (ETC) consists of four large multi-protein complexes that are
embedded in the inner mitochondrial membrane. Hydrogen is acquired by complexes I and II
from NADH and FADH2, respectively. The electrons are then passed down the chain to complex
IV, which transfers them to molecular oxygen; the reduced oxygen then reacts with protons to
yield water. Complexes I, III and IV extract energy from the electron flow and use it to expel
protons across the membrane. For each electron migrating down the chain, multiple protons are
pumped out of the mitochondrion.
The protons accumulated outside the mitochondrion are allowed back in through another
membrane protein, namely, ATP synthase. This protein is a molecular motor, driven to rotate by
the flow of protons through it into the mitochondrial matrix. The rotary motion of ATP synthase
in turn drives the synthesis of ATP from ADP and phosphate. As mentioned before, the porins in
the outer mitochondrial membrane are permeable for most small molecules and ions, and thus
the proton concentration in the space between the two mitochondrial membranes equilibrates
readily with the cytosol. The proton concentration gradient that powers ATP synthesis therefore
exists across the inner mitochondrial membrane only.
THE ENERGETICS AND CHEMIOSMOTIC HYPOTHESIS OF ETC
Complex I, Complex III and Complex IV pump protons across the inner
mitochondrial membrane
– pumping uses the energy liberated from the oxidation of NADH and FADH2
– pumping generates a membrane potential because it generates an
electrochemical gradient
• negative inside, positive outside
• alkaline inside, acidic outside
THE CHEMIOSMOTIC HYPOTHESIS
•A proton concentration gradient serves as the energy reservoir for driving ATP
formation
• Electron transport through the ETC generates a proton gradient (pumps H+
from the matrix to the intermembrane space)
•Protonmotive force (p) is the energy of the proton concentration
gradient
• Protons that are translocated into the intermembrane space by electron
transport, flow back into the matrix via ATP synthase
– H+ flow forms a circuit (similar to an electrical circuit)
• The transmembrane protein, ATP synthase, catalyzes the phosphorylation of ADP in
a reaction driven by movement of H+ across the inner membrane into the matrix
• As protons move back into the matrix through ATP Synthase, the energy stored
in the electrochemical proton gradient is used to make ATP
• Passage of protons through the Fo (stalk) into the matrix is coupled to ATP formation
• Estimated passage of 3 H+ / ATP synthesized
• Fo is sensitive to oligomycin, an antibiotic that binds in the channel and blocks H+
passage, thereby inhibiting ATP synthesis
ATP yield of complete glucose oxidation
The amount of ATP gained in the respiratory chain for each molecule of glucose degraded is
large, but it cannot be calculated with complete precision and varies between different
physiological states.
Theoretical ATP per molecule of glucose completely oxidized
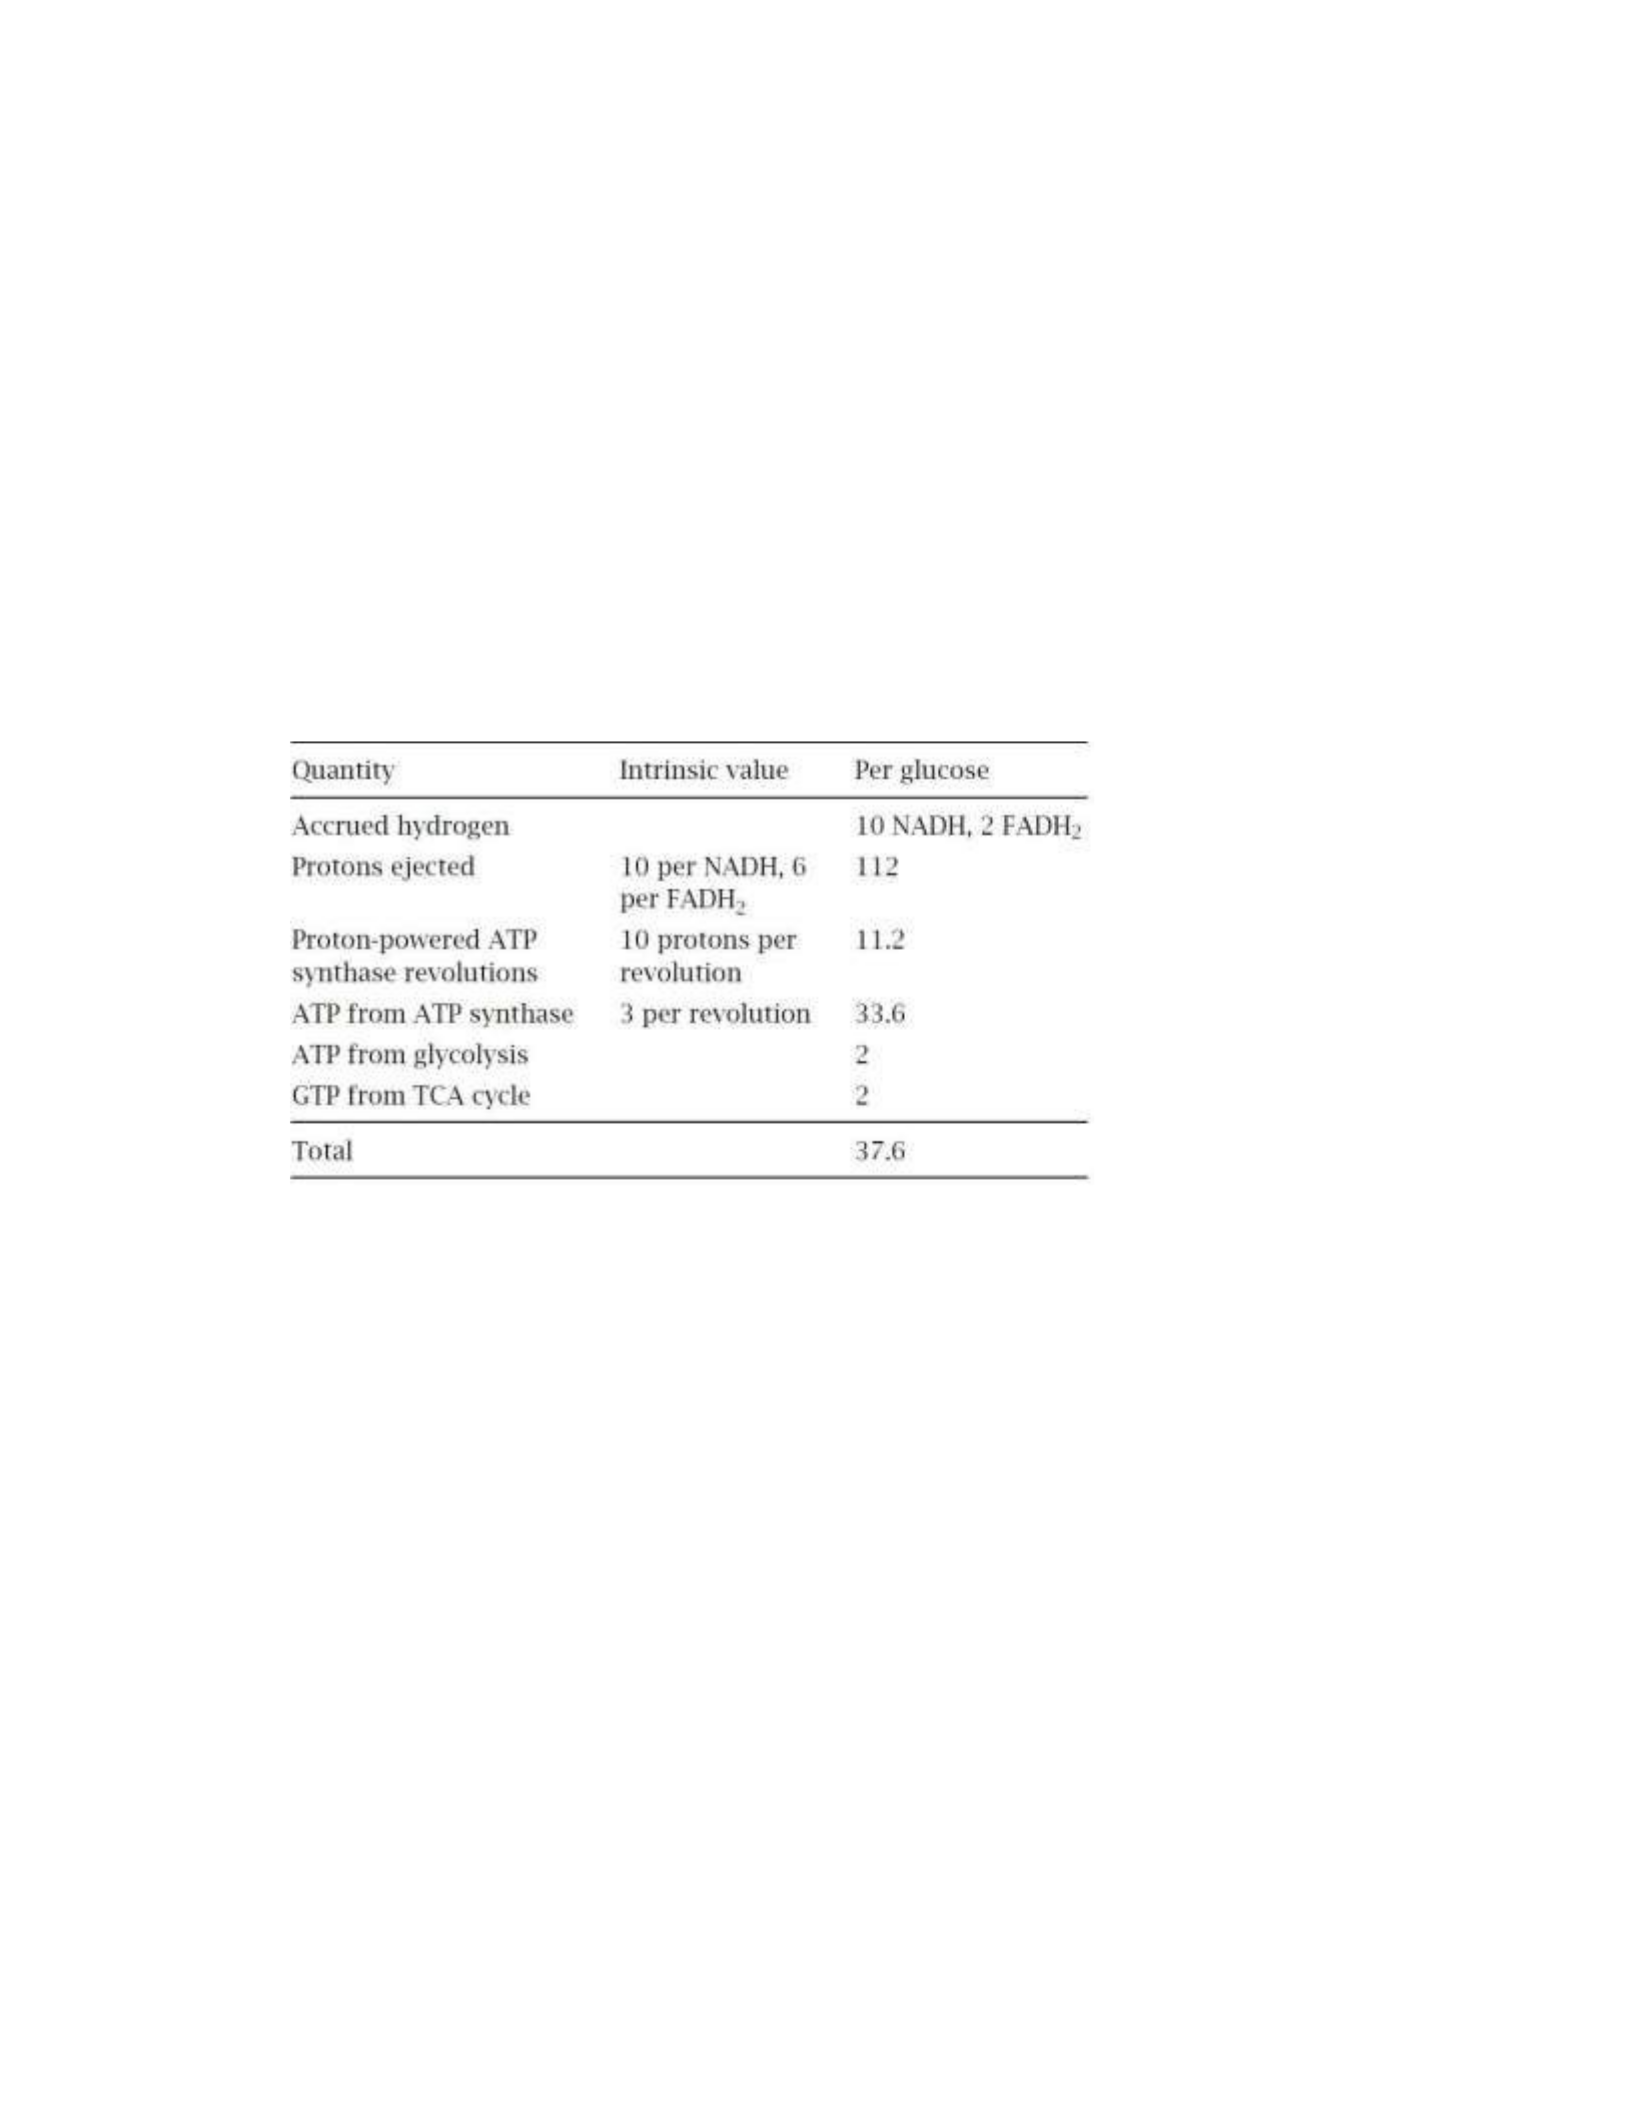
Notes: The number of NADH molecules given here includes all molecules accruing in glycolysis,
pyruvate dehydrogenase, and the TCA cycle. The numbers of protons pumped per molecule of
NADH are based on the assumption that complexes I, III, and IV pump 4, 2, and 4 protons,
respectively. GTP, which is formed in the succinate thiokinase reaction in the TCA cycle, is
energetically equivalent to ATP.
The P:O Ratio
molecules of ADP phosphorylated
P:O ratio = - -
atoms of oxygen reduced
• Translocation of 3H+ required by ATP synthase for each
ATP produced

• 1 H+ needed for transport of Pi, ADP and ATP
•Net: 4 H+ transported for each ATP synthesized
Calculation of the P:O ratio
Complex I III IV #H+
translocated/2e- 4 4 2
Since 4 H+ are required for each ATP
synthesized: For NADH: 10 H+
translocated / O (2e-)
P/O = (10 H+/ 4 H+) = 2.5 ATP/O
For succinate substrate = 6 H+/
O (2e-) P/O = (6 H+/ 4 H+) =
1.5 ATP/O
RESPIRATORY INHIBITORS & UNCOUPLERS:
Inhibitors are chemicals that can block electron transfer through
specific complexes in the ETC
•Complex I: blocked by rotenone, barbiturates
•Complex III: blocked by antimycin A
•Complex IV: blocked by cyanide, azide, carbon monoxide
Uncouplers
• In some special cases, the coupling of the two processes can be disrupted.
•Uncouplers stimulate the oxidation of substrates in the absence of ADP
• Large amounts of O2 are consumed but no ATP is produced.
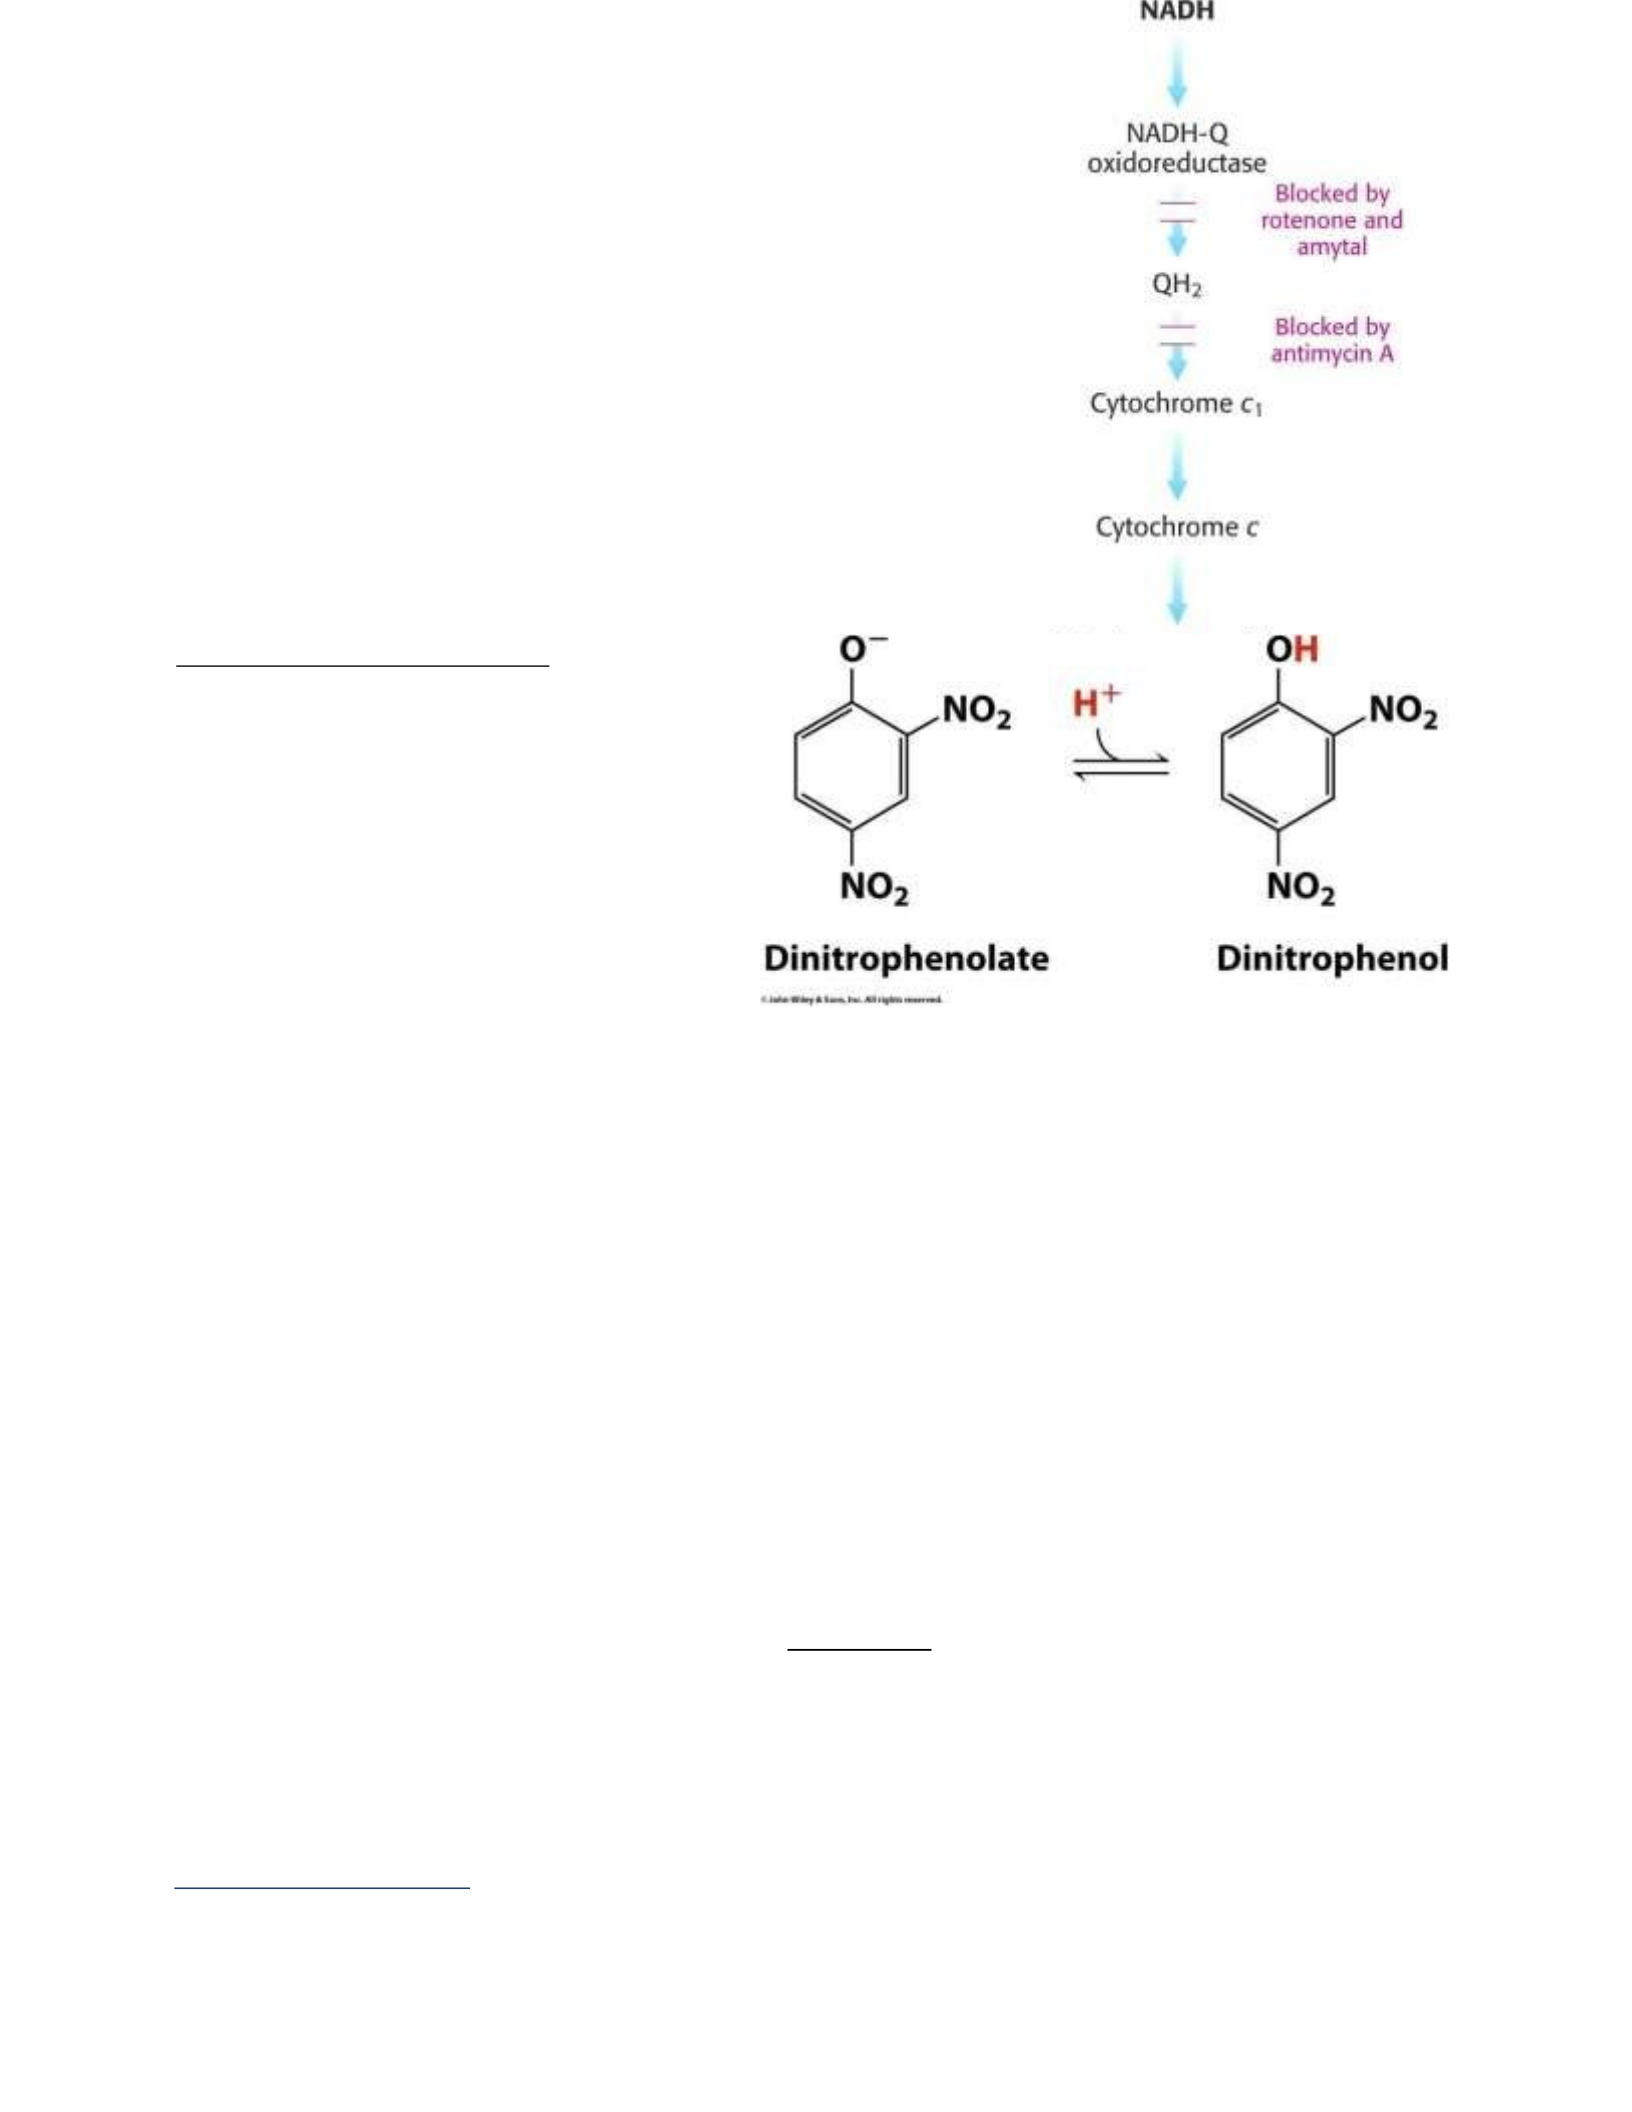
• Uncouplers are lipid-soluble weak acids
• Both acidic and basic forms can cross the inner
mitochondrial membrane
• Uncouplers deplete any proton gradient by transporting
protons across the membrane
• Do NOT affect electron transport
• Allow protons back into the matrix without making ATP
• Stimulate oxygen consumption
2,4-Dinitrophenol: an uncoupler
• Used as a diet/weight loss drug
• Hydrophobic low molecular
weight substance that can diffuse
through the mitochondrial inner
membrane
• Shuttles protons across the
membrane and dissipates proton
gradient
• ATP synthesis goes down
– ADP concentration in cells goes up and acts as a stimulator
– Signals to turn on pathways to make ATP
– Therefore, electron transport and O2 consumption turned on fully and is NOT
regulated
• Energy produced by electron transport released as HEAT rather than harnessed into ATP
synthesis
• Fuels (carbs and fats) are consumed at great rates and get quick weight loss BUT
– Get heavy breathing – using lots of oxygen
– Excessive fever (heat generation)
– BIG problem – no control over uncoupling
– Brain, heart and muscles are affected as well
• 2,4-dinitrophenol is extremely toxic and pulled from the market
NATURAL UNCOUPLERS
• In newborn and hibernating animals, brown fat oxidizes large amounts of substrate
(mostly fatty acids) to generate heat
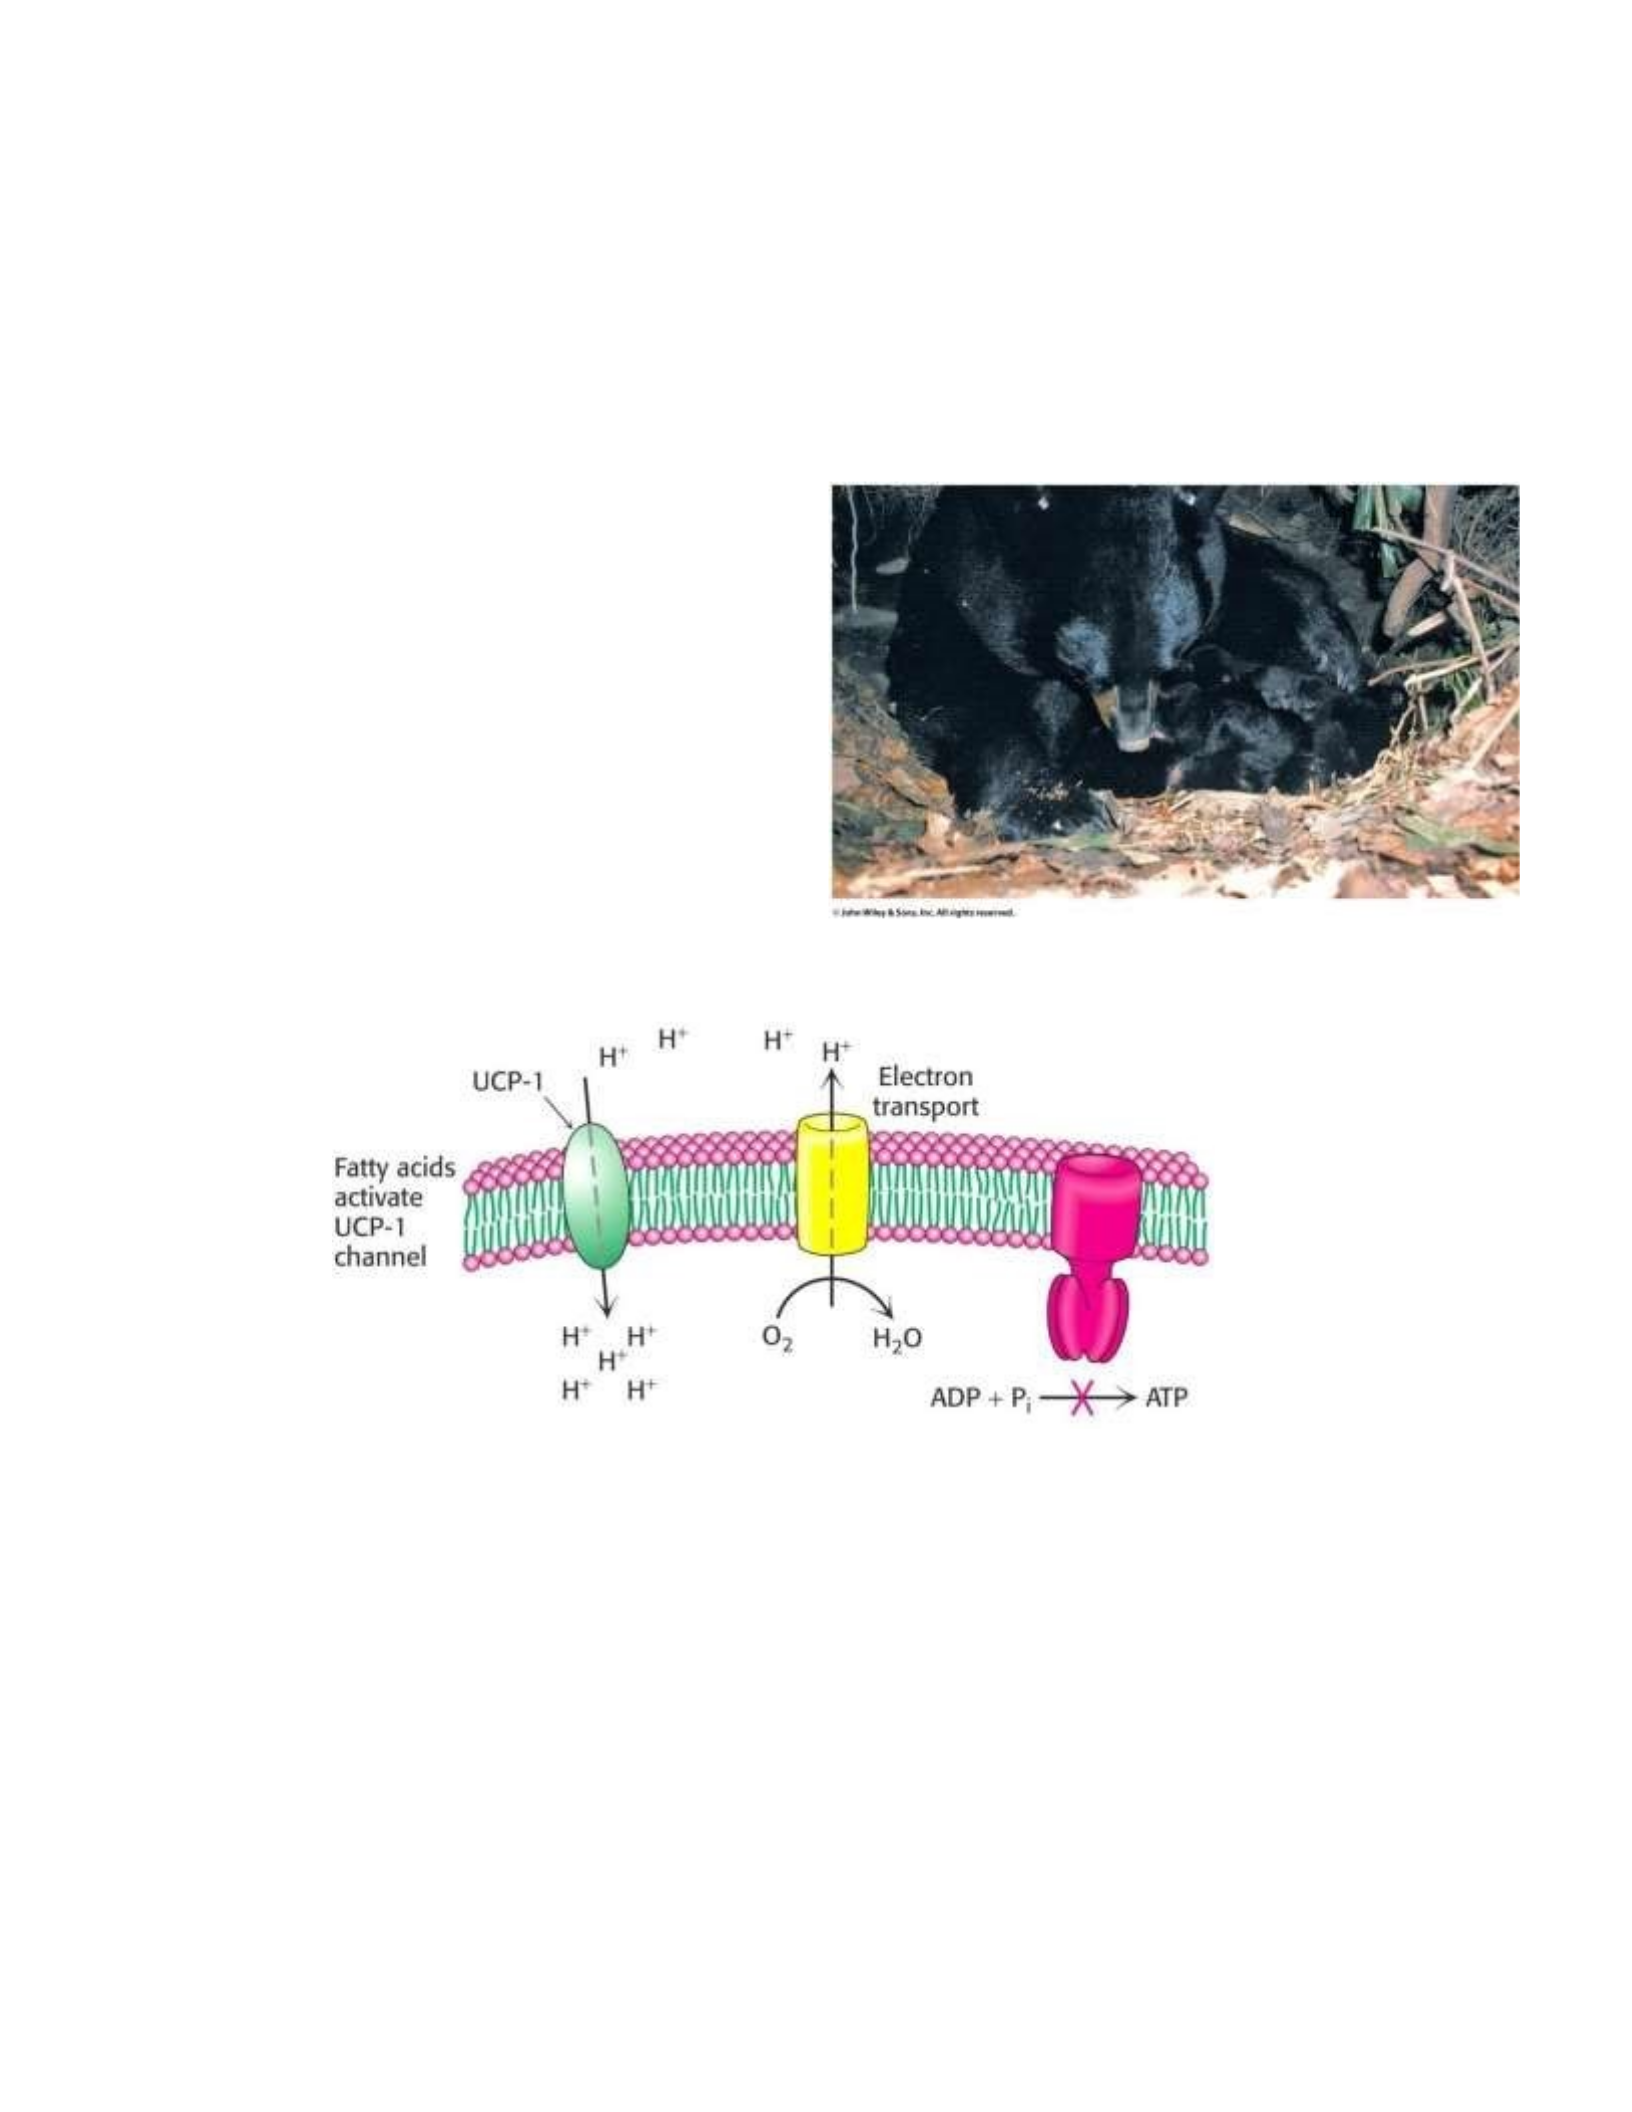
• ‘Brown fat’- brown because of the large number of mitochondria and their associated
cytochromes
• In brown fat mitochondria oxidation of NADH and FADH2 is uncoupled from ATP
synthesis
– Mitochondria contain thermogenin (uncoupling protein).
– Thermogenin allows the release of energy as heat instead of ATP.
–Thermogenin
dissipates proton
electrochemical
gradient
• By providing another channel for return
of protons - bypasses ATP synthase
• Also called uncoupling protein (UCP)
•In brown fat mitochondria, the energy that
would have been used to make ATP is liberated as heat
GLYCOGEN METABOLISM
Overview
In addition to gluconeogenesis, the reversible storage of glucose in the form of glycogen
provides a second major mechanism of glucose homeostasis. Glycogen is a glucose polymer that
is found in many organs, but the largest quantities occur in the liver and in skeletal muscle. The
liver can store up to 150–200 grams. It draws from this reservoir to maintain the blood glucose
concentration; glycogen plays a major role in day-to-day glucose homeostasis.
While the concentration of glycogen in muscle is lower than in the liver, the approximately ten
times greater overall mass of skeletal muscle means that the absolute amount of glycogen stored
there is approximately twice higher than in the liver. The contribution of muscle glycogen to
glucose homeostasis is less well understood.

Glycogen synthesis and degradation
The regular, periodic structure of glycogen corresponds to similarly regular and periodic methods
of synthesis and breakdown that require only a modest number of enzymes. The following
enzyme reactions occur in glycogen synthesis:
Synthesis:
1. Synthesis of an activated precursor, UDP-glucose, by UTP-glucose-1-phosphate
uridylyltransferase
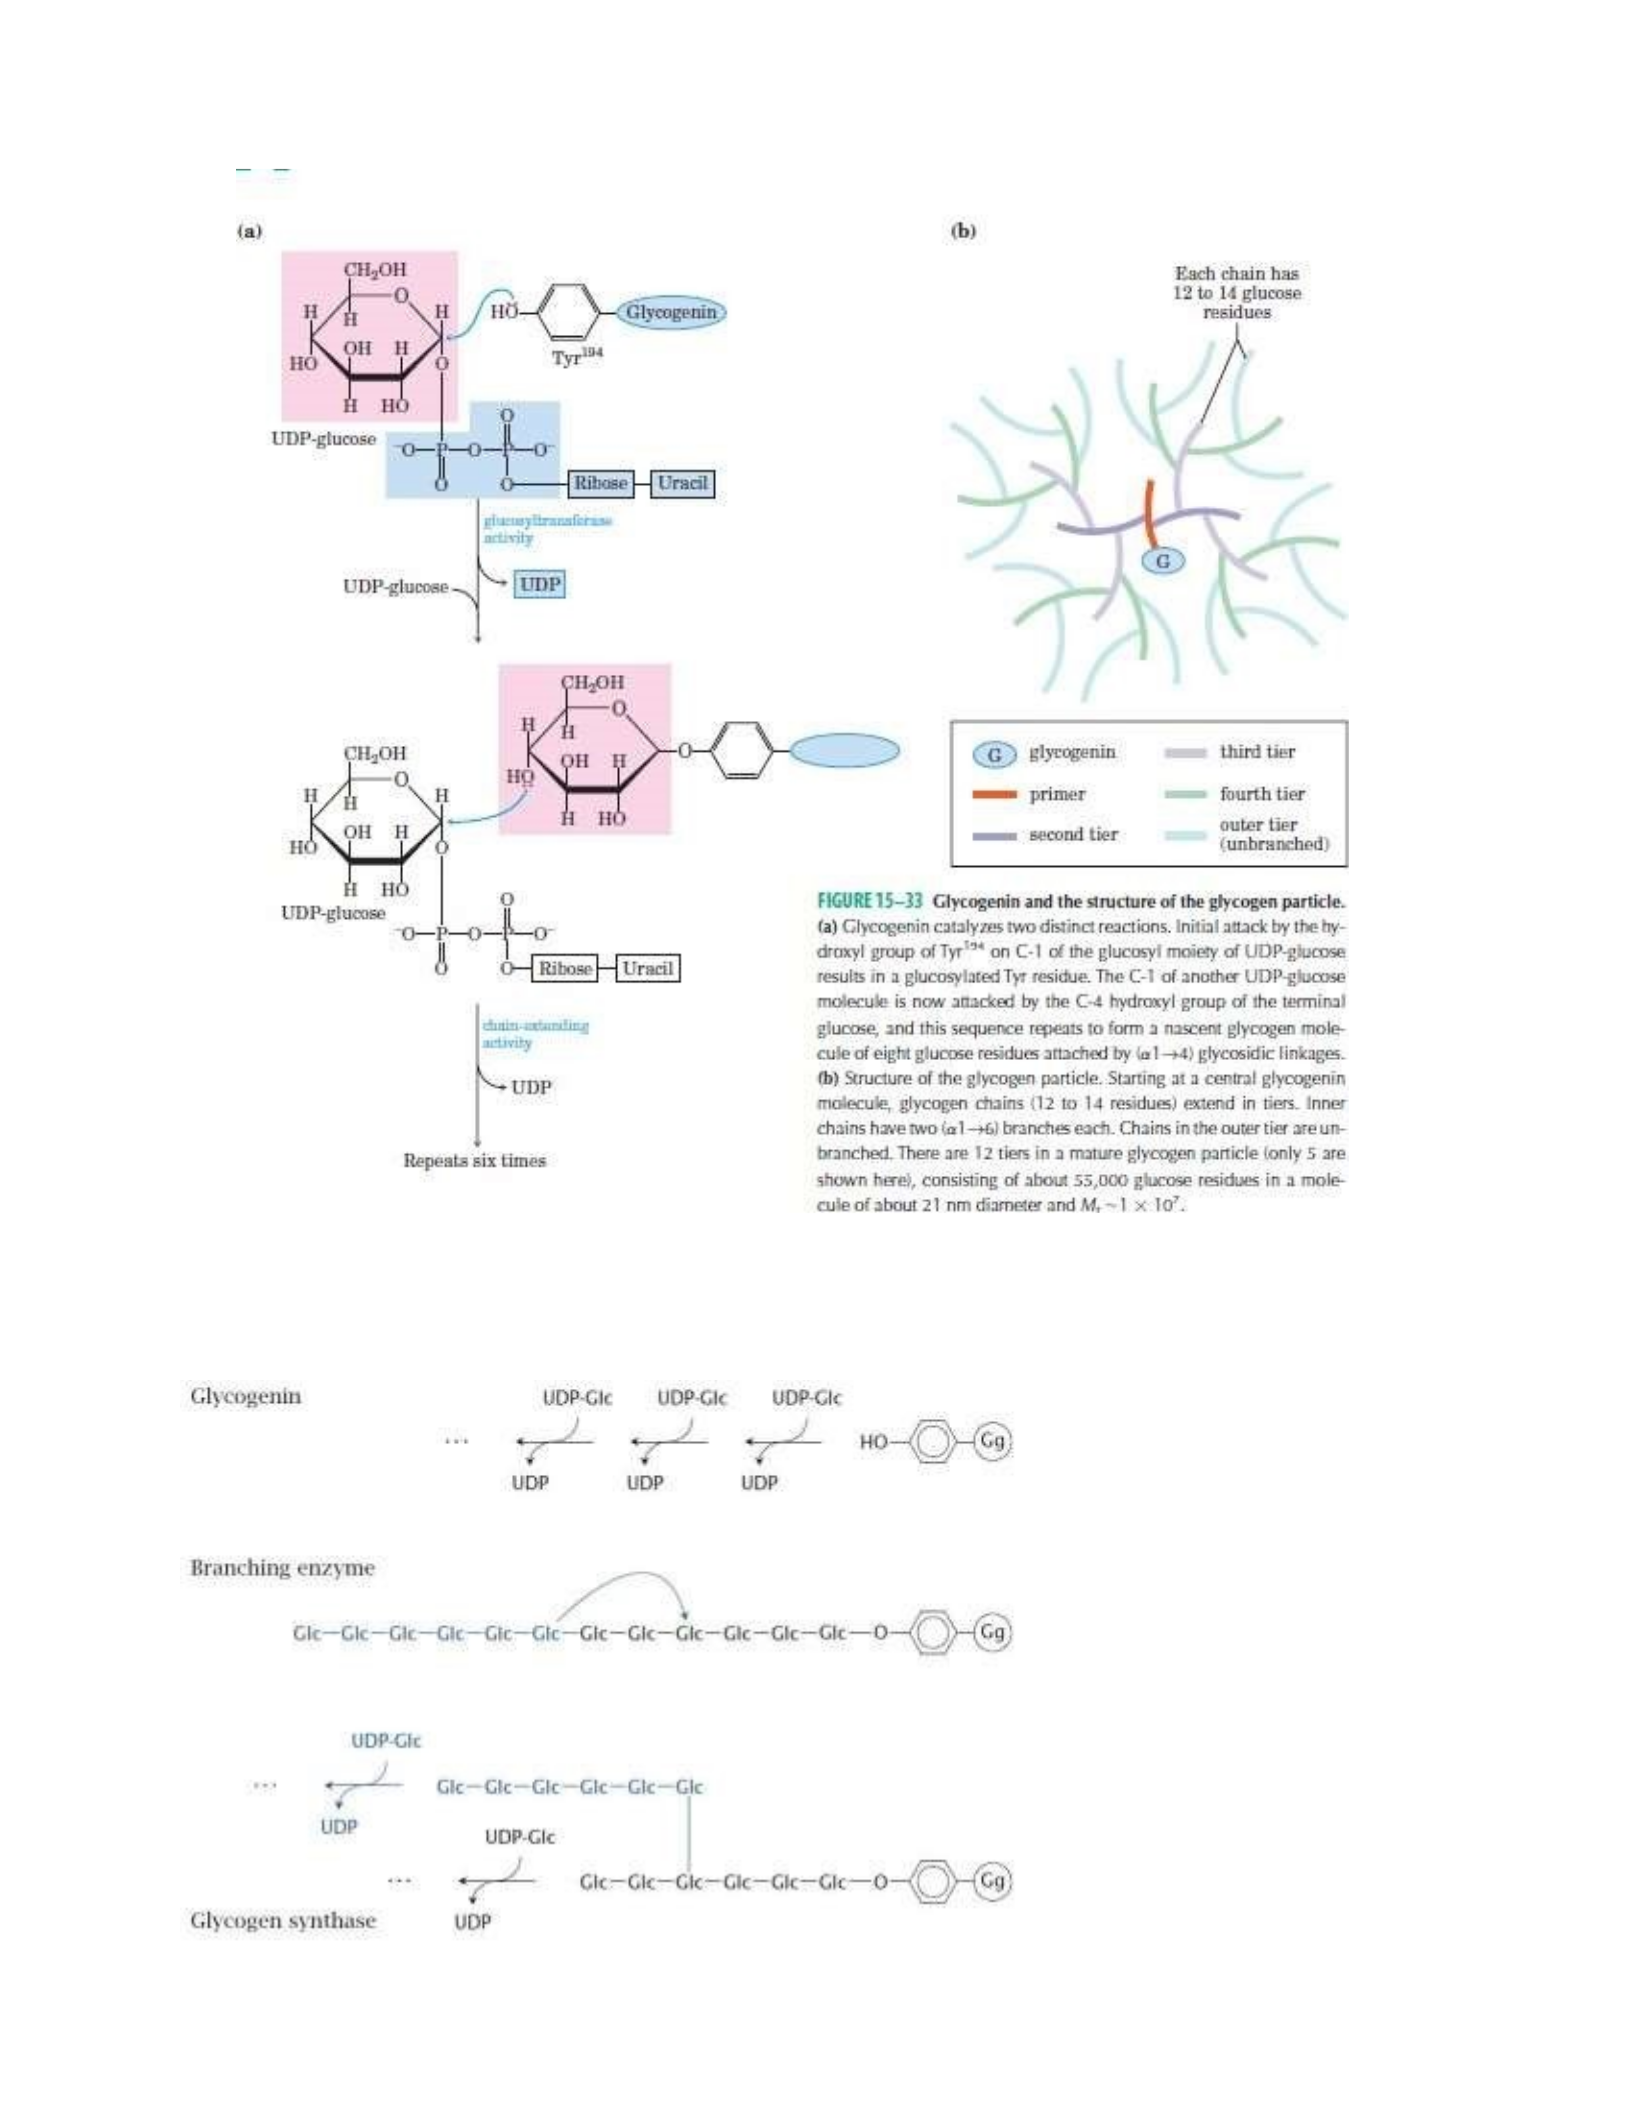
2. Initiation of glycogen synthesis by glycogenin
3. Introduction of branches by branching enzyme
4. Chain elongation by glycogen synthase
5. Repeat steps 3 and 4
Degradation:
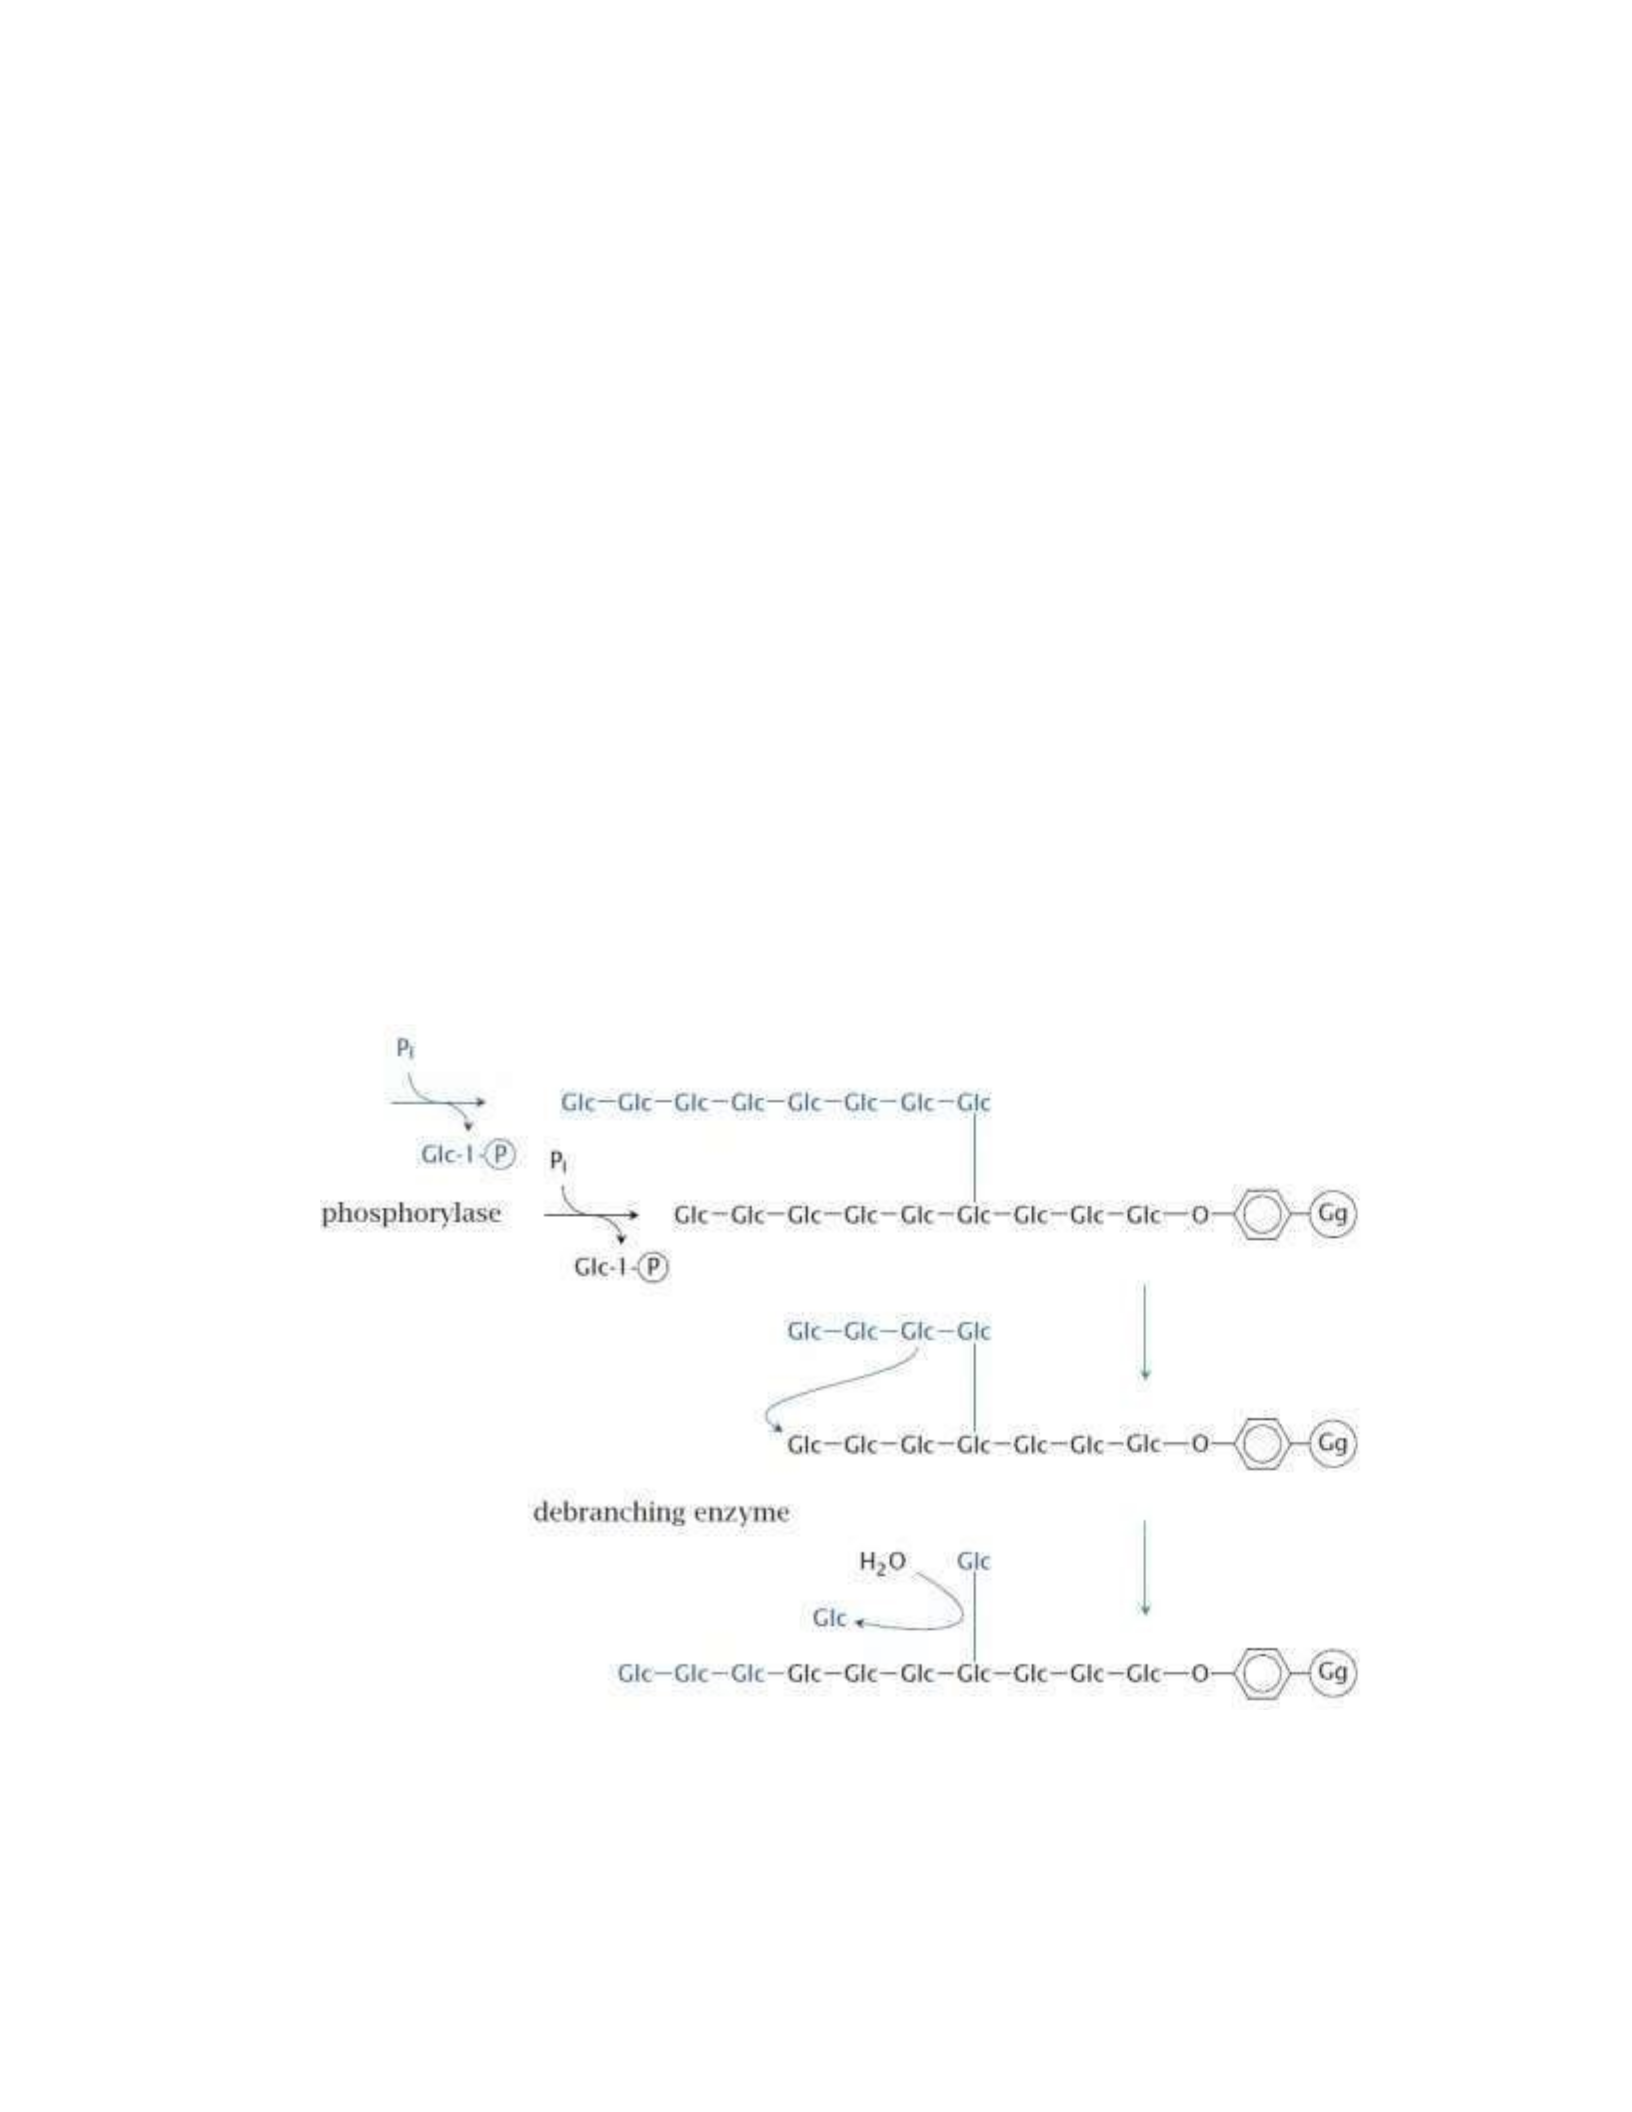
1. Depolymerization of linear strands by phosphorylase
2. Removal of branches by debranching enzyme 3. Repeat steps 1 and 2
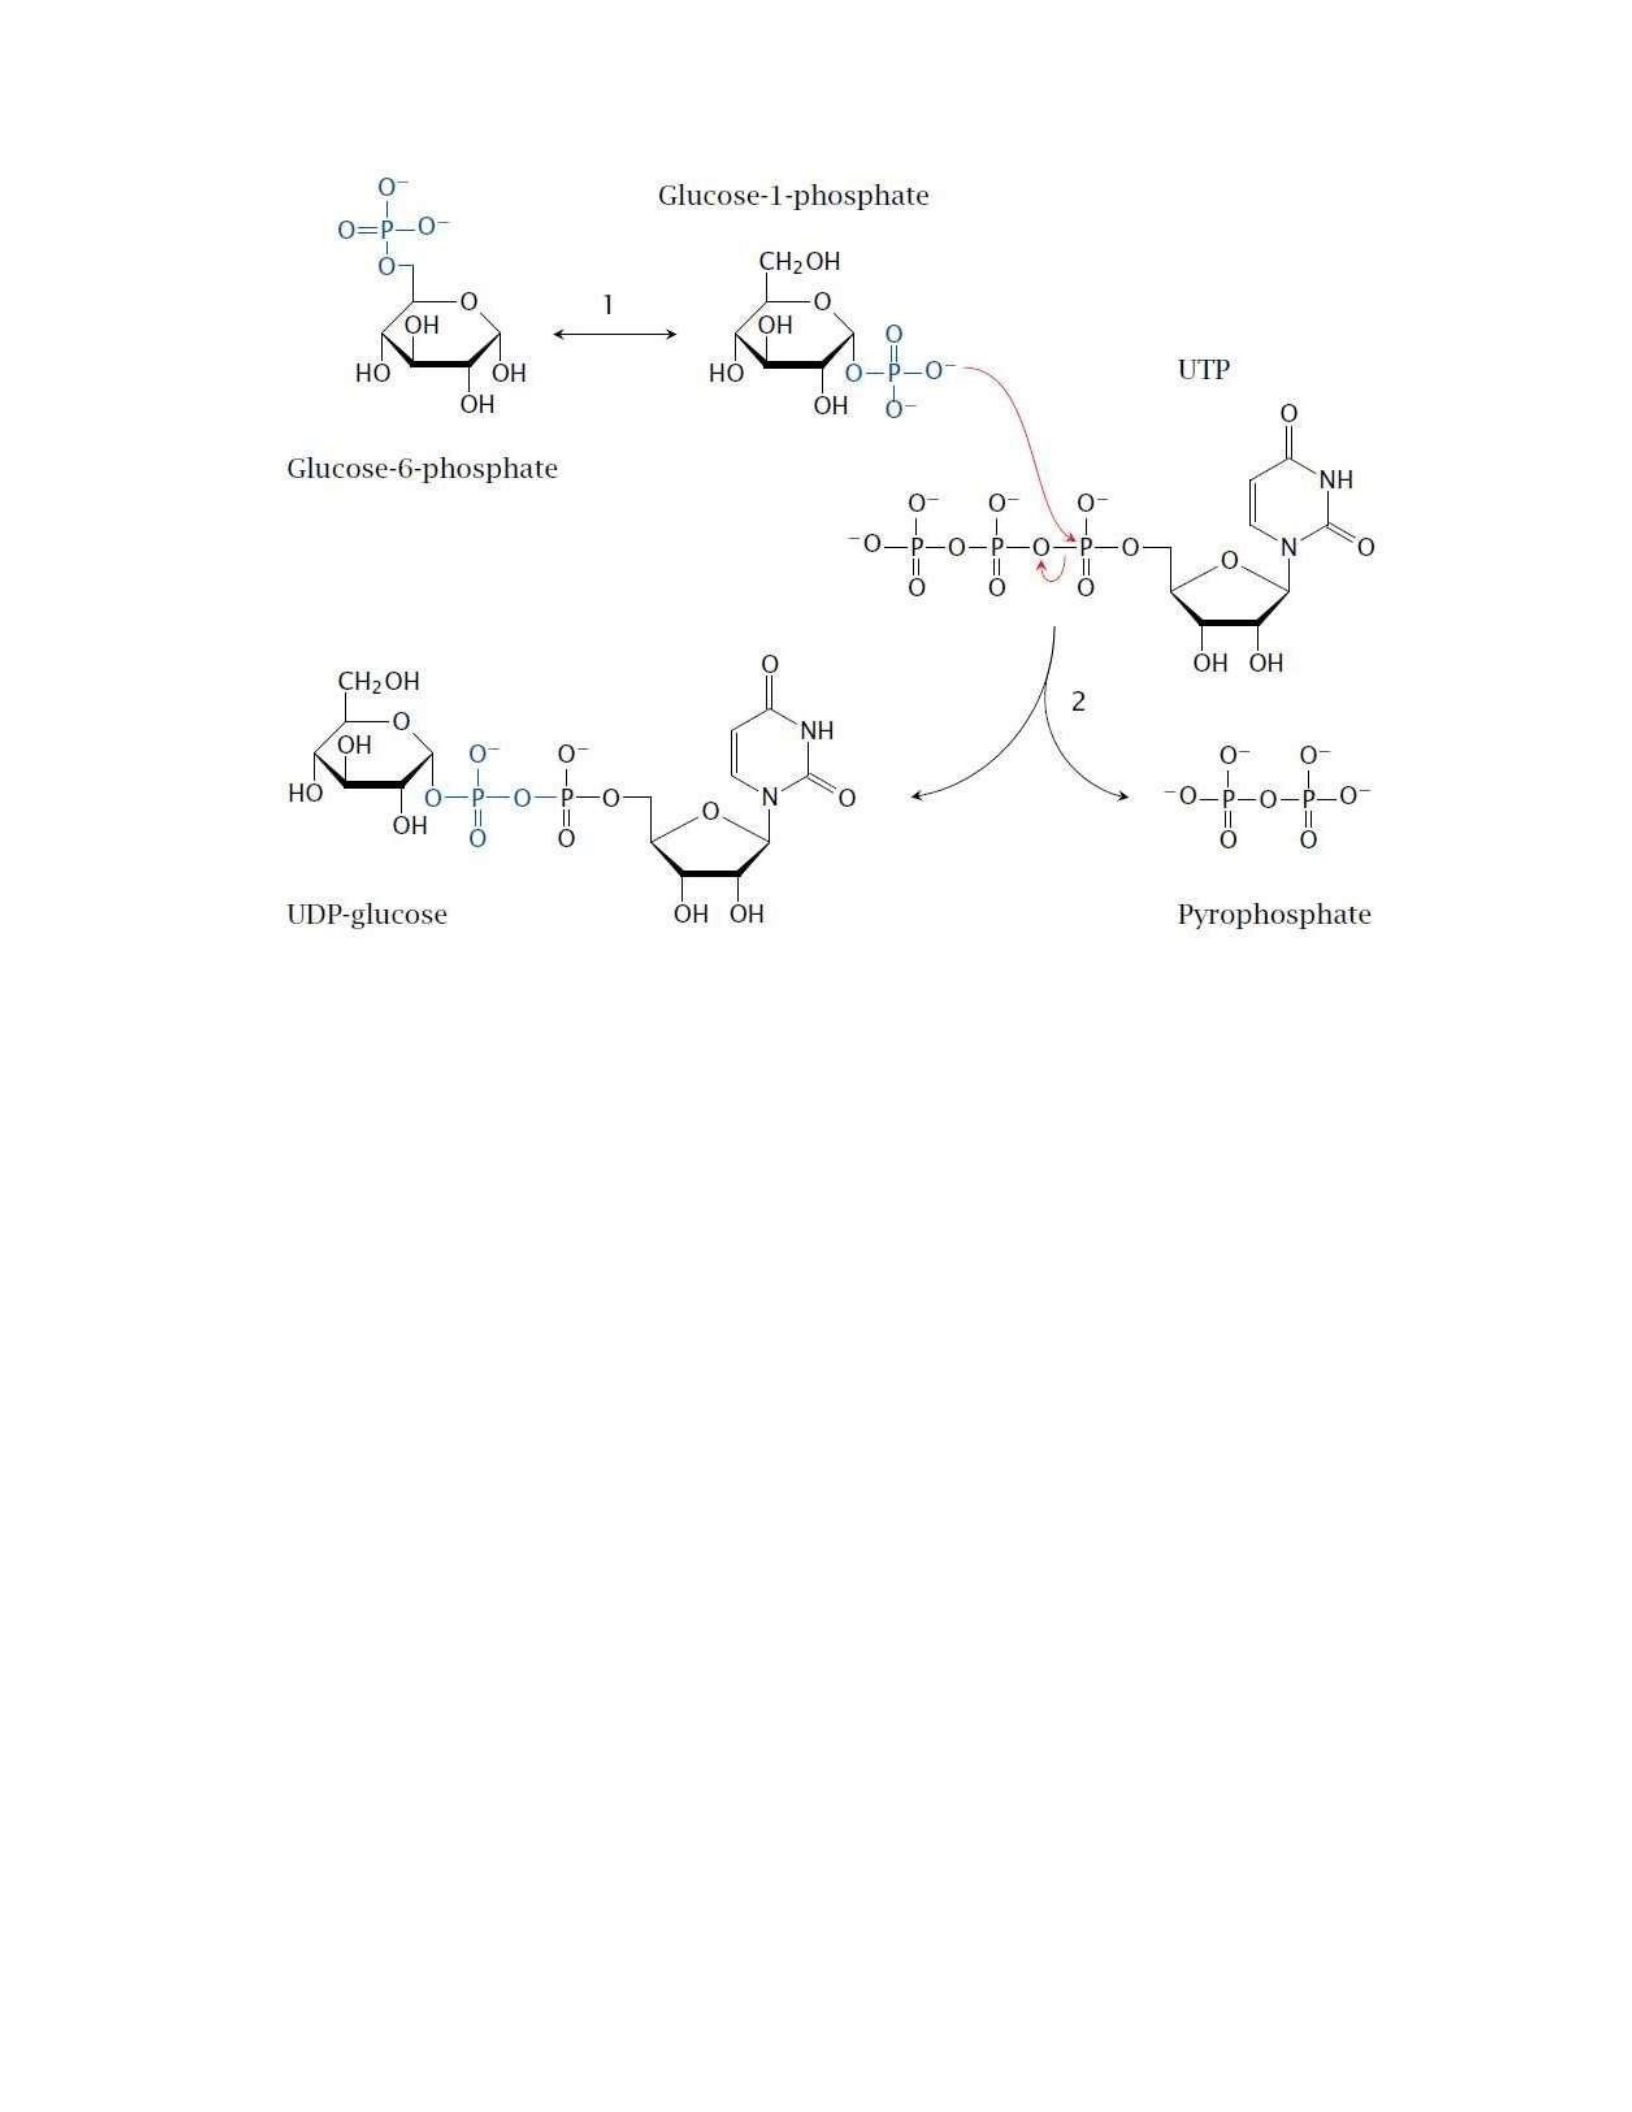
Activation of glucose for glycogen synthesis
Notes: Both glycogenin and glycogen synthase use an activated form of glucose, UDP-glucose,
which is formed from glucose-6-phosphate in two steps. Phosphoglucomutase first transforms
glucose-6-phosphate to glucose-1-phosphate (1), which is then converted to UDP-glucose by
glucose-1-phosphate uridylyltransferase (2). The latter reaction requires uridine triphosphate
(UTP) and releases pyrophosphate.3 The UDP-glucose that is used in the Leloir pathway of
galactose degradation is derived in the same manner. UDP-glucose is also the precursor of UDP-
glucuronic acid, which is used in the conjugation of bilirubin and of xenobiotics.
Overview of glycogen synthesis
Glycogenin Primes the Initial Sugar Residues in Glycogen
Glycogen synthase cannot initiate a new glycogen chain de novo. It requires a primer, usually a
preformed (_1→4) polyglucose chain or branch having at least eight glucose residues. So, how is
a new glycogen molecule initiated? The intriguing protein glycogenin is both the primer on
which new chains are assembled and the enzyme that catalyzes their assembly.
The first step in the synthesis of a new glycogen molecule is the transfer of a glucose residue
from UDP-glucose to the hydroxyl group of Tyr194 of glycogenin, which is catalyzed by the
protein’s intrinsic glucosyltransferase activity. The nascent chain is extended by the sequential
addition of seven more glucose residues, each derived from UDP-glucose; the reactions are
catalyzed by the chain-extending activity of glycogenin. At this point, glycogen synthase takes
over, further extending the glycogen chain. Glycogenin remains buried within the β-particle,
covalently attached to the single reducing end of the glycogen molecule.
Overview of glycogen degradation
Notes: Glycogen degradation is brought about by phosphorylase and debranching enzyme. All
glucose residues that are joined by α-1 4-glycosidic bonds—that is, those in the straight
segments—are released by glycogen phosphorylase. Most enzymes that cleave glycosidic bonds
simply hydrolyze them; examples are intestinal amylase and β-galactosidase. In contrast,
glycogen phosphorylase employs phosphate ions instead of water, and so produces glucose-1-
phosphate instead of free glucose. Glucose- 1-phosphate is then converted to the mainstream
metabolite glucose-6-phosphate by phosphoglucomutase.
In the liver, which stores glycogen for the benefit of the entire body, the lion’s share of glucose-
6- phosphate will be dephosphorylated by glucose-6-phosphatase and then released into the
circulation; overall, this is equivalent to outright hydrolysis. However, muscle uses glycogen
largely toward its own energy needs, and therefore glucose-6- phosphate will usually be funneled
straight into glycolysis. In this case, the use of phosphorolysis instead of hydrolysis bypasses the
hexokinase reaction, thereby saving one equivalent of ATP.
Glycogen phosphorylase only degrades the chain ends to within four residues of a branching
point. Then, debranching enzyme takes over and transplants the stub to another free end, where it
becomes again a substrate for phosphorylase. However, debranching enzyme leaves behind a
single residue attached by a α-1 6-glycosidic bond, which it subsequently releases as free
glucose through hydrolysis.
Lysosomal glycogen disposal
•concerns a minor fraction of glycogen
•key enzyme: acid maltase; enzyme defect causes slow but inexorable glycogen accumulation
•possible role: disposal of structurally aberrant glycogen particles that have become “tangled
up” during repeated cycles of glucose accretion and depletion
Notes: In liver cells, approximately 10% of all glycogen particles are found inside lysosomes,
where they undergo slow degradation by acid maltase. This enzyme catalyzes the same reactions
as intestinal amylase and maltase but has an acidic pH optimum, in keeping with the acidic
environment inside lysosomes (pH~4.5). The lysosomal degradation pathway is important for the
disposal of structurally aberrant glycogen particles; additional metabolic roles may exist but are
currently not well understood. An enzyme defect for lysosomal maltase causes Pompe’s disease.
Inter-organ relationships in glycogen metabolism
As stated above, the two tissues that have the most significant pools of glycogen are the liver and
skeletal muscle. Liver glycogen is turned over rapidly; it serves as the major reserve of blood
glucose during short-term fasts. Once liver glycogen is depleted, muscle glycogen can be drawn
down; this, however, requires some roundabout metabolic trickery.
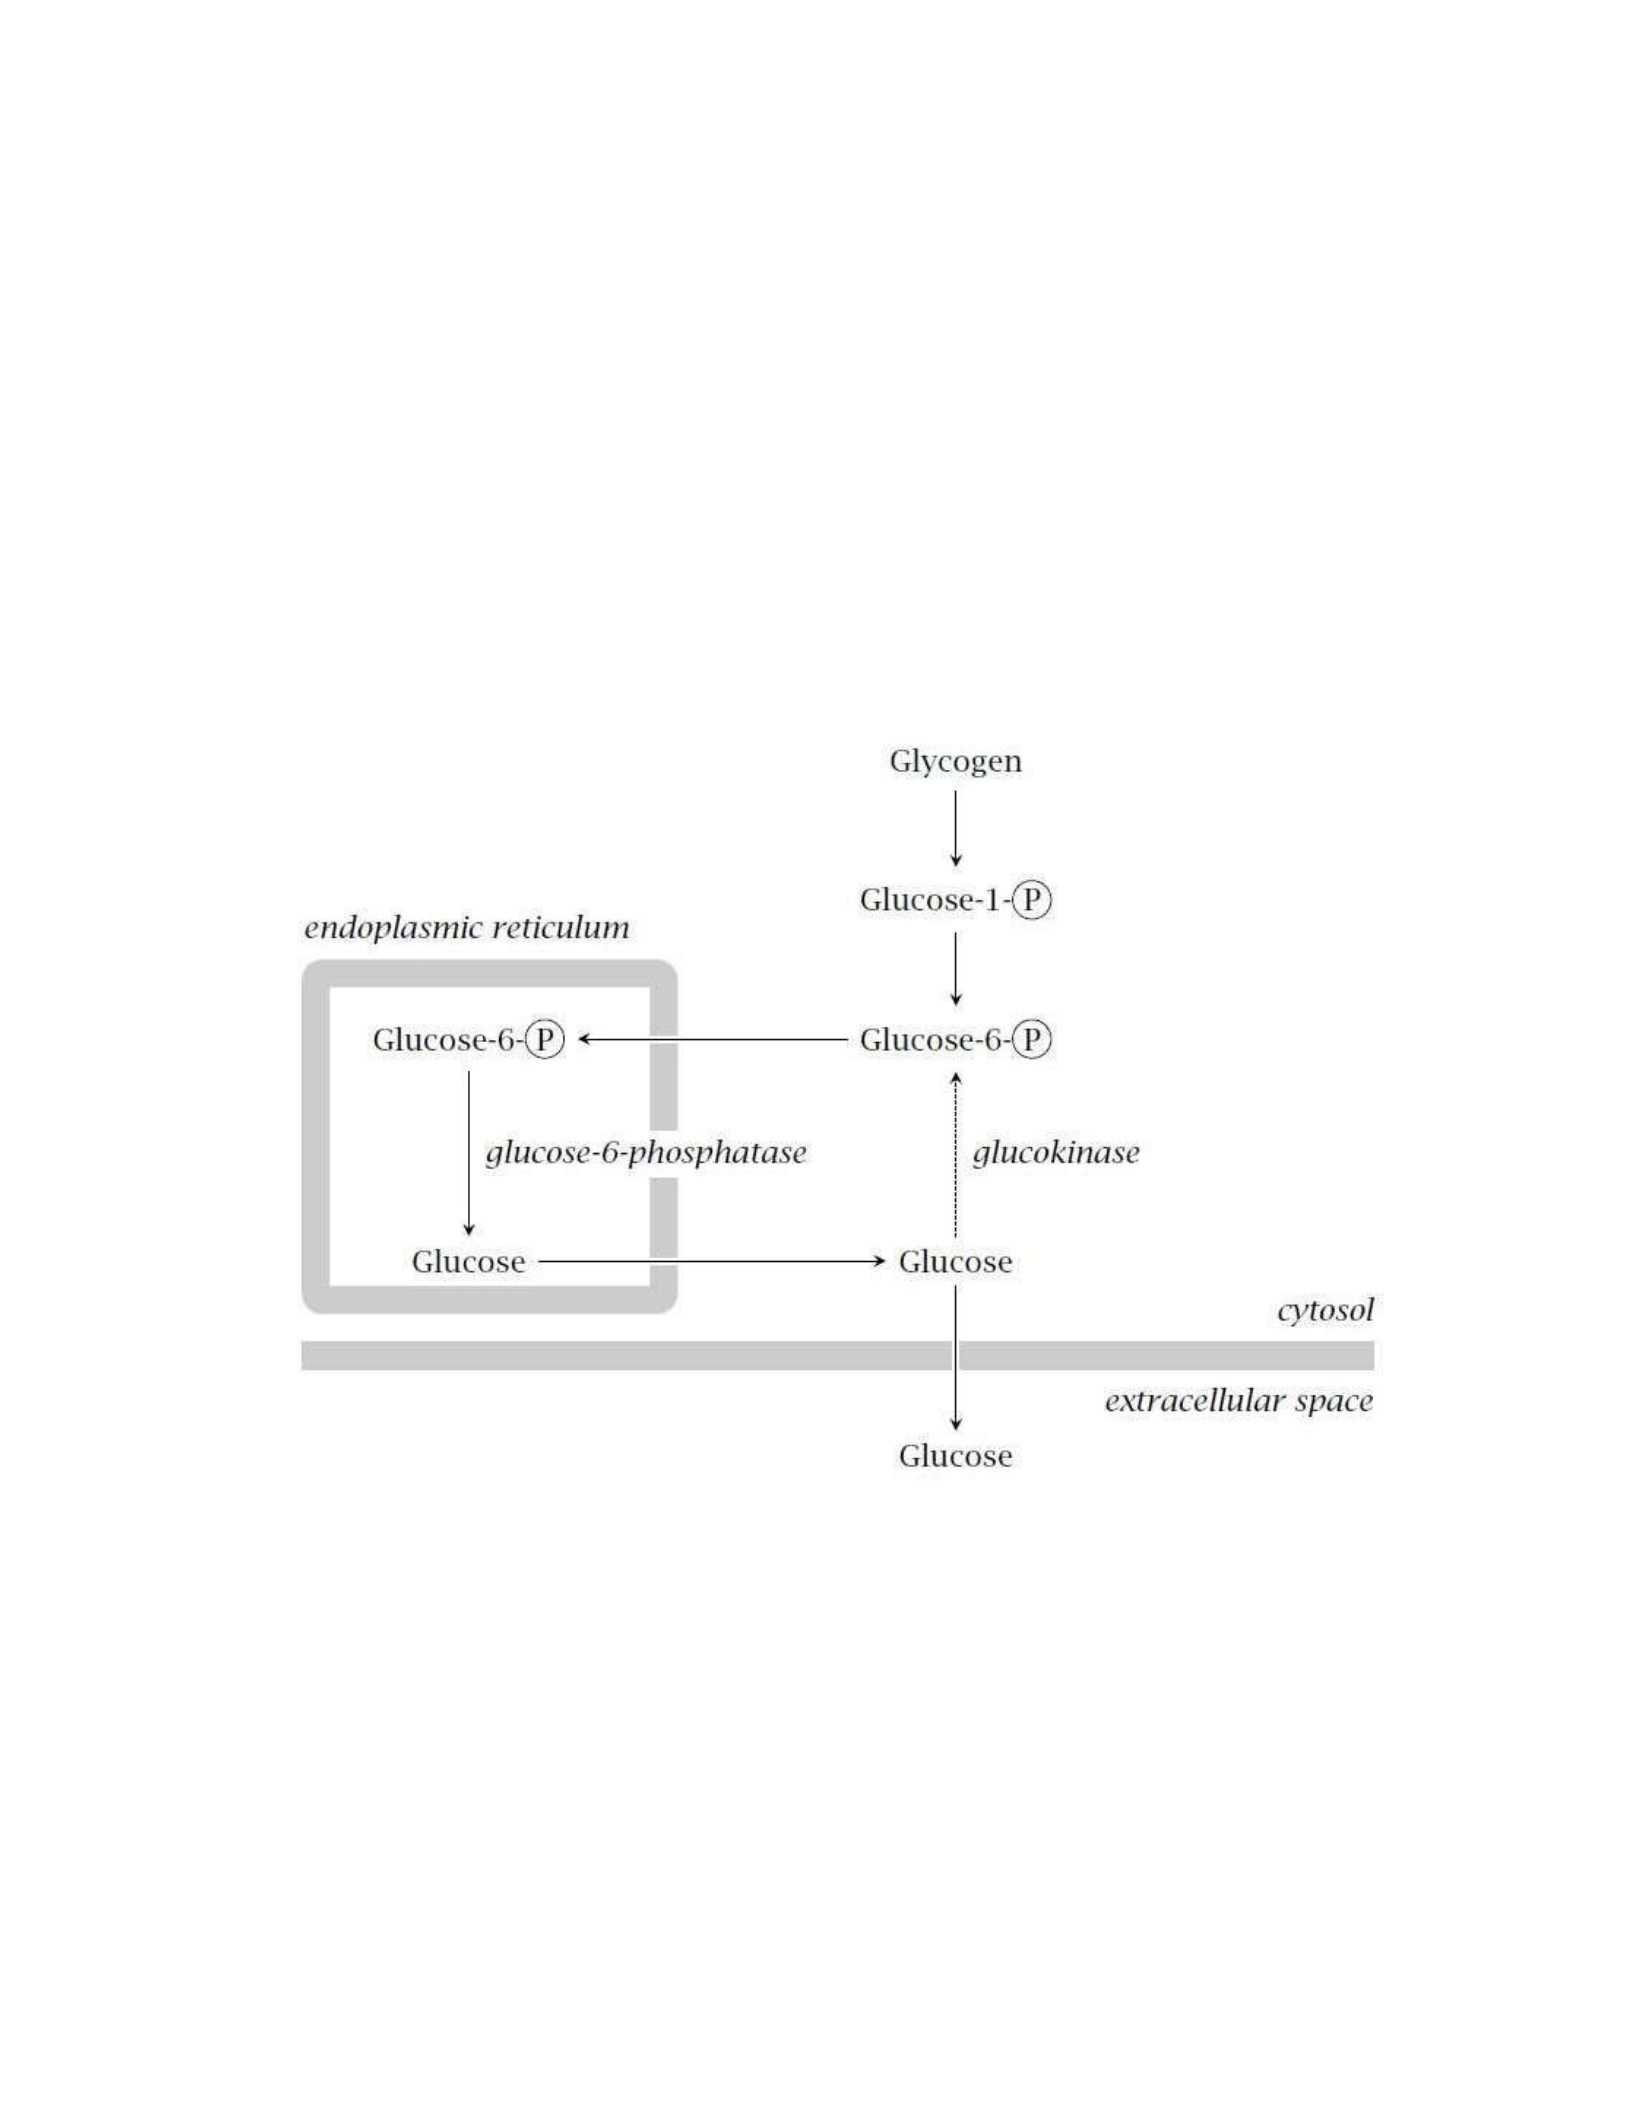
Liver glycogen utilization
Notes: The liver mobilizes glucose from its glycogen store via glycogen phosphorylase and
phosphoglucomutase, which yields glucose-6-phosphate. The latter is transported to the
endoplasmic reticulum, where it is dephosphorylated. Glucose is taken back to the cytosol and
released into the bloodstream. Some of the glucose will be rephosphorylated, creating the futile.
However, the dominant glucose phosphorylating enzyme in the liver is glucokinase, which has
fairly low affinity for glucose; therefore, enough glucose will escape rephosphorylation and be
released into the bloodstream.
Muscle glycogen utilization
Notes: Muscle glycogen primarily serves the energy needs of muscle tissue itself; during
prolonged physical exercise, most of it is broken down to glucose-6-phosphate and then
consumed via the usual pathways right within the cells that stored it. As discussed above, this
usage is facilitated by calcium-mediated activation of glycogen phosphorylase.
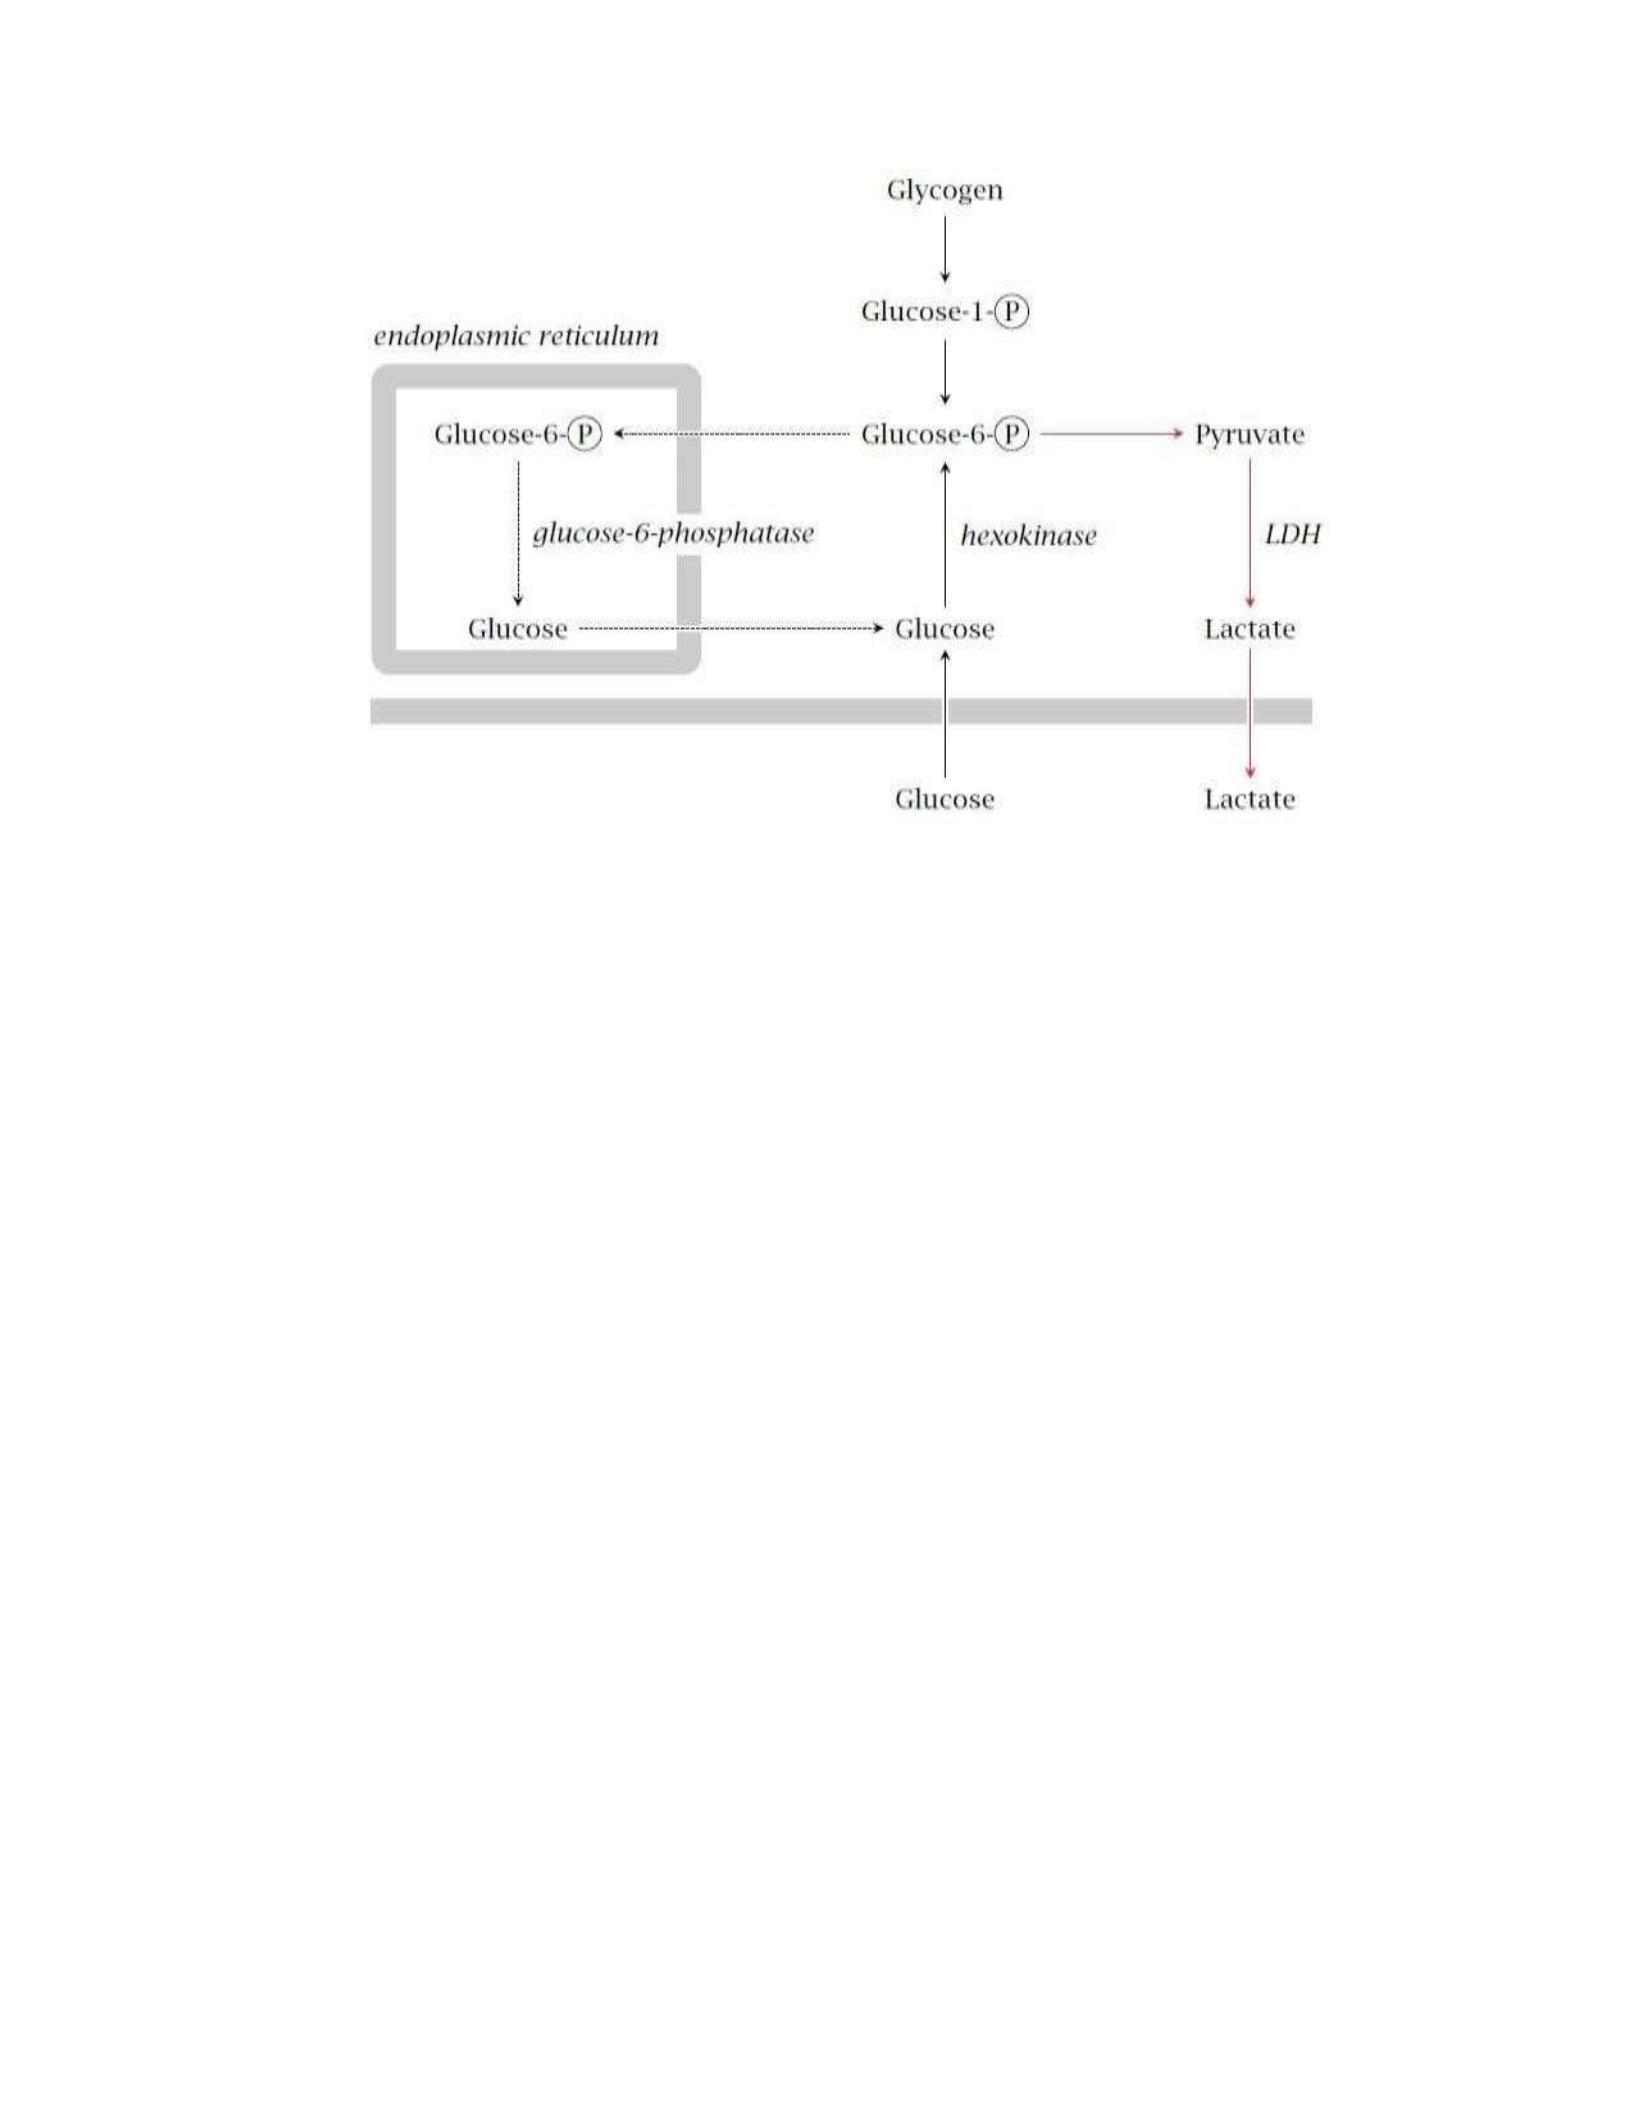
Under suitable conditions, namely, prolonged fast without physical exercise, muscle glycogen
can also contribute to the replenishment of blood glucose. However, even though muscle cells
have been shown to express glucose-6-phosphate and are therefore, in principle, able to produce
free glucose, they should find it difficult to release it. This is because muscle contains
hexokinase, which has a much greater substrate affinity than glucokinase and therefore will keep
the intracellular level of free glucose well below the extracellular concentration. The net
transport of glucose should therefore be directed inward at all times; this agrees with all the
physiological evidence I could find.
The way around this obstacle is to convert glucose-6-phosphate to pyruvate and then lactate. At a
low rate, lactate formation occurs even in resting muscle and under aerobic conditions. This
lactate is derived in various proportions from blood glucose and glycogen, respectively. In
animal experiments, epinephrine promotes glycogen utilization and lactate release, but overall
the hormonal control of this process and the magnitude of its contribution to systemic glucose
control are not well characterized.
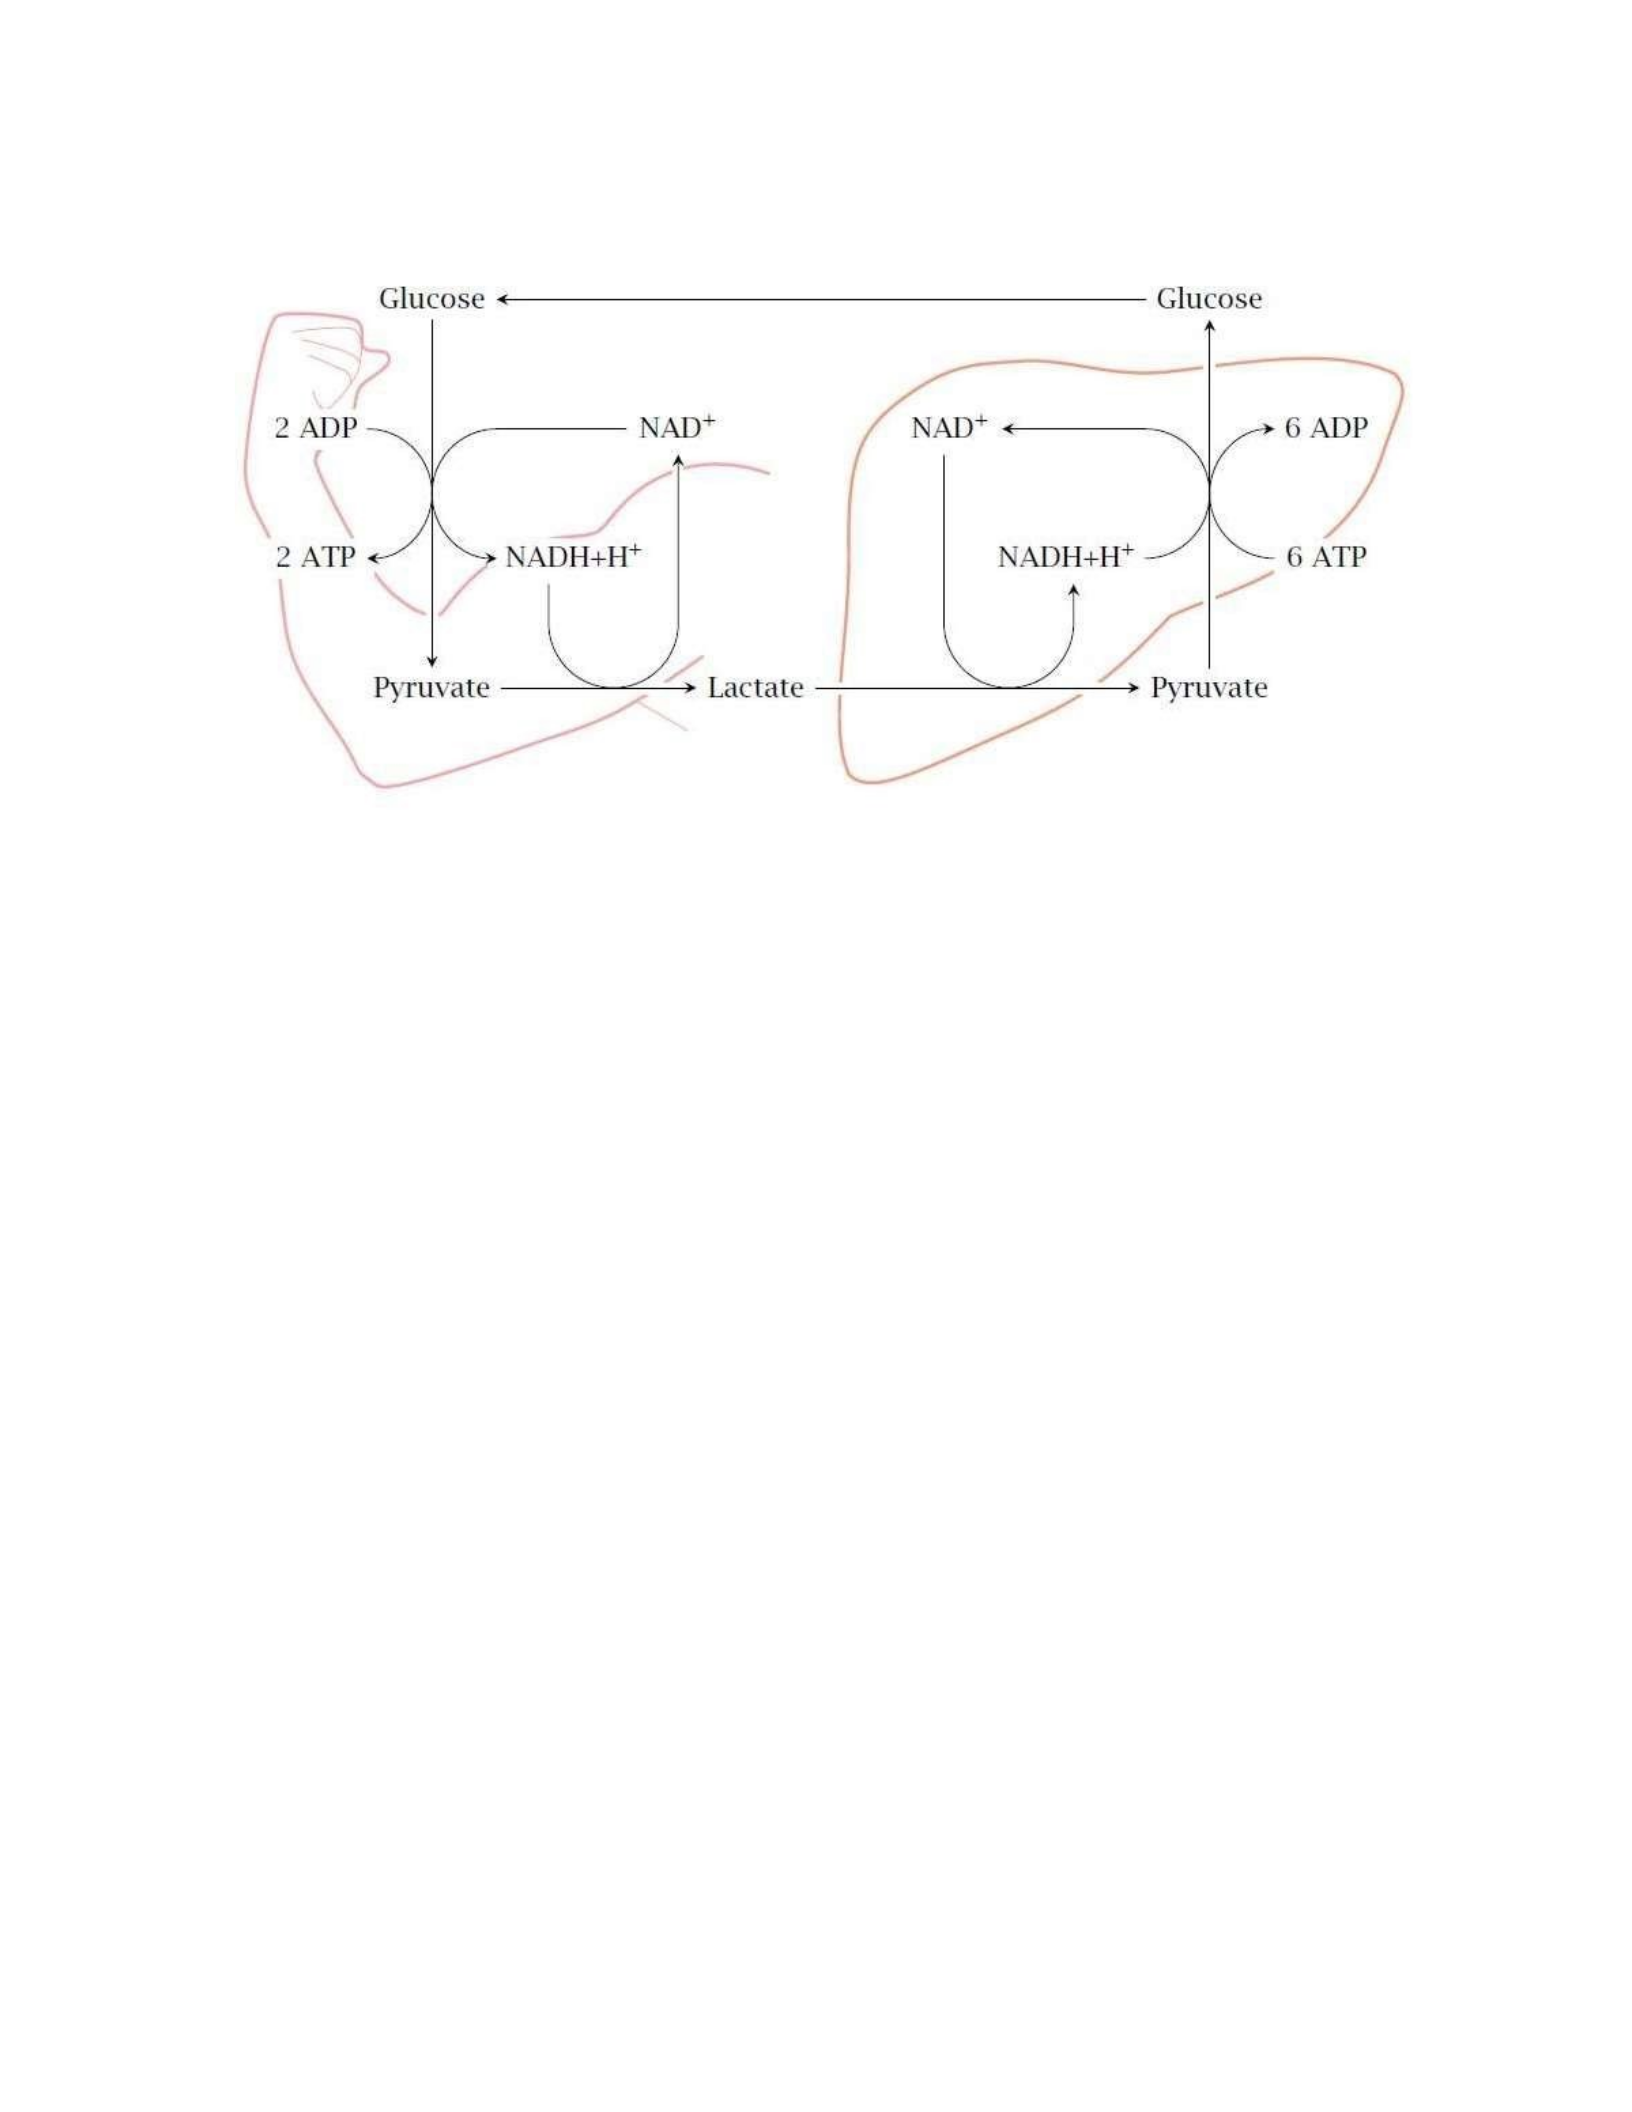
The Cori cycle
Notes: While skeletal muscle relies on oxidative metabolism most of the time, some other
tissues, notably red blood cells and lymphocytes, which collectively account for some 4 kg of
cell mass, depend mostly or even exclusively on anaerobic glycolysis even under aerobic
conditions. The lactate released in peripheral tissues is scooped up by the liver, which converts it
back to glucose through gluconeogenesis. This process is known as the Cori cycle, named after
its discoverers Carl and Gerti Cori, who worked it out as early as 1929.
Skeletal produces lactate at a very much higher rate during short bouts of maximal exercise when
the ATP demand exceeds the capacity for aerobic metabolism. Some textbooks state the Cori
cycle resupplies the muscle with glucose in this situation also. This, however, is quite impossible.
During intense exercise, the cardiac blood output is diverted from the visceral organs to skeletal
muscle. Therefore, when ATP demand exceeds the oxygen supply of skeletal muscle, the oxygen
shortfall would be even greater in the liver, should it indeed attempt to make enough ATP for
sustaining the muscle through gluconeogenesis; and even with sufficient oxygen, its capacity for
making glucose would fall far short of the muscles’ voracious appetite.
Anaerobic exercise can be sustained for only short periods of time anyway. During this period,
the lactate turned out by skeletal muscle will simply accumulate; it will then slowly be scooped
up by the liver and turned back into glucose after we have collapsed at the side of the track to
catch our breath.
Glycogen storage diseases
Genetic defects have been described for several enzymes of glycogen metabolism. The clinical
syndromes associated with these defects are referred to as glycogen storage diseases. While these
conditions are not particularly common, they do shed some light on the physiological
significance of glycogen metabolism. Some conditions are clinically severe and are the focus of
ongoing therapeutic research. Several examples are briefly discussed below.
Glucose-6-phosphatase deficiency (von Gierke disease)
•Glucose formed in gluconeogenesis or released from glycogen cannot be exported from liver
and kidney cells
•Glycogen builds up in liver and kidneys
•Severe hypoglycemia
•Lactic acidosis
•Hyperlipidemia
•Hyperuricemia
Notes: Gluconeogenesis and glycogen degradation in liver and kidneys produce glucose-6-
phosphate, which must then be dephosphorylated to glucose in order to be exported into the
bloodstream. An enzyme defect for glucose-6-phosphatase prevents glucose release, which
causes abnormally low blood glucose levels (hypoglycemia). Some of the surplus glucose
accumulates as glycogen, whereas the remainder is converted to pyruvate in glycolysis and either
emerges as lactate or, downstream of pyruvate dehydrogenase, is turned into triacylglycerol and
cholesterol; the excess lactate and lipids account for the observed lactic acidosis and
hyperlipidemia.
The causation of hyperuricemia—excess blood levels of uric acid, is less obvious. During
episodes of hypoglycemia, the liver will be intensely stimulated by glucagon and epinephrine
and make a forceful but futile attempt to mobilize its stored glycogen. The large amount of
glucose-6- phosphate produced in this attempt, which cannot be converted to glucose, ties up and
depletes cellular phosphate. This impedes the regeneration of ATP and raises the level of AMP,
some of which then enters degradation to uric acid.
The clinical severity of this disease may vary, presumably due to different levels of residual
enzyme activity. Some cases may be managed with a diet of frequent, starch-rich meals, which
helps to avoid hypoglycemia. In more severe cases, liver transplantation may become necessary.
Acid maltase deficiency (Pompe disease)
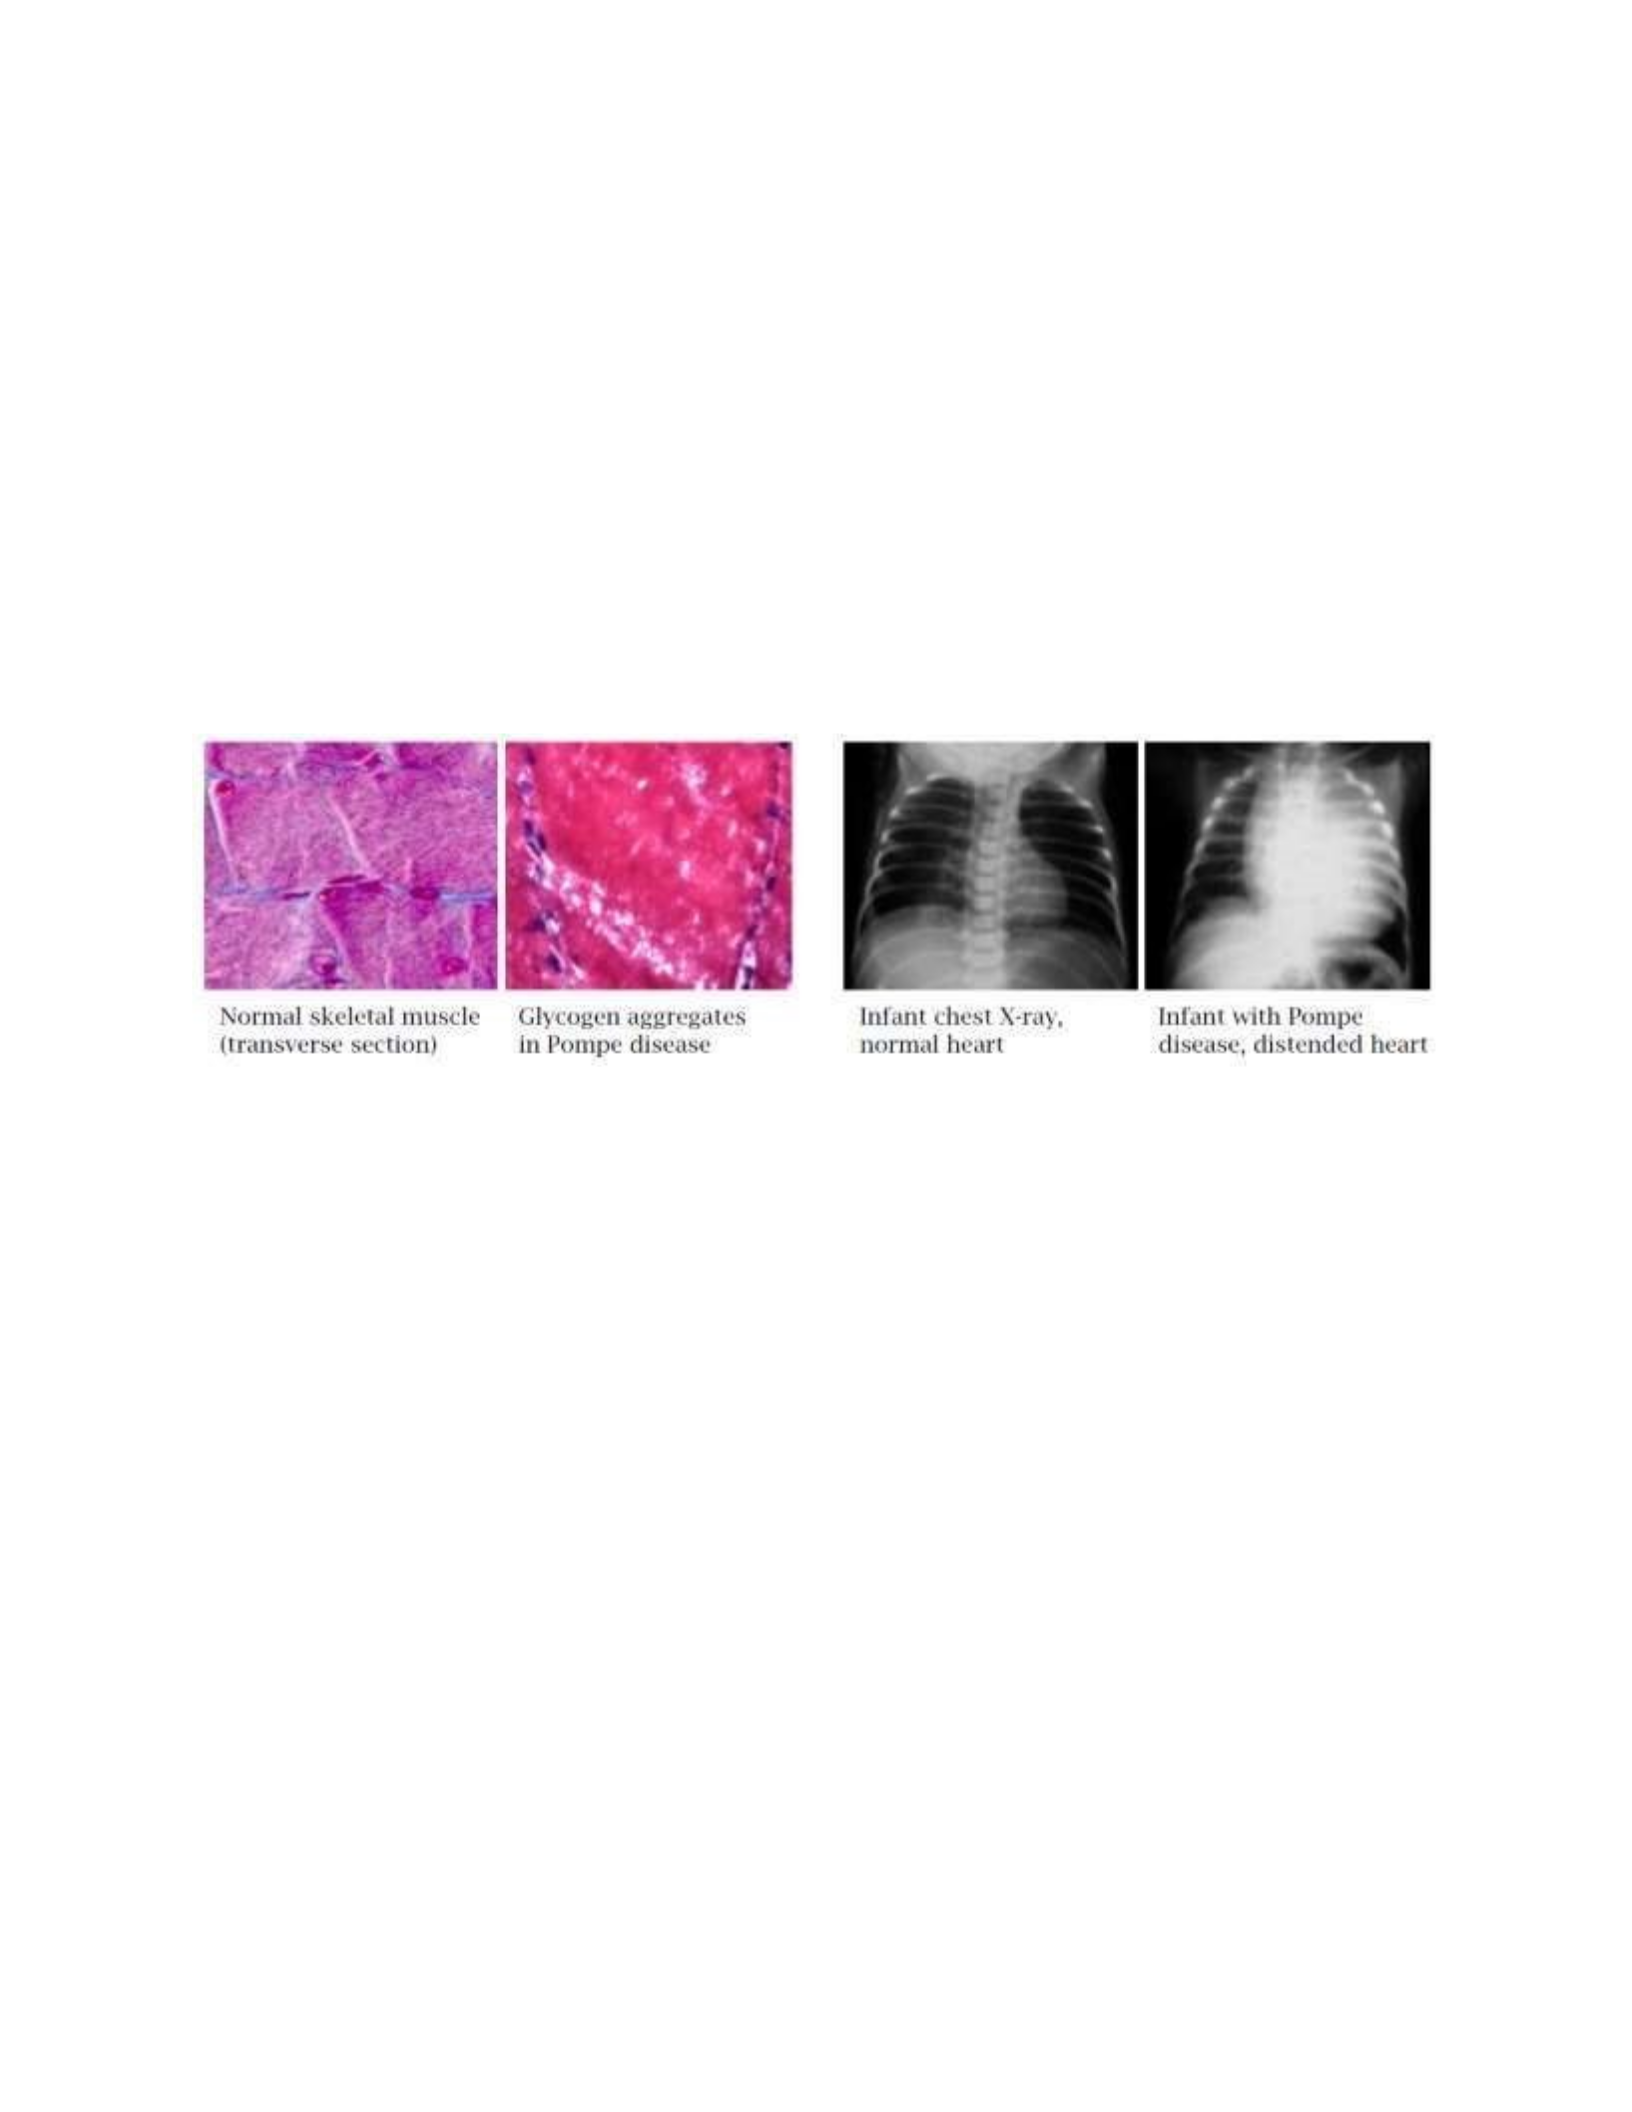
Notes: A homozygous deficiency of acid maltase disrupts lysosomal glycogen degradation and
results in glycogen accumulation. Skeletal and heart muscle are more strongly affected than the
liver. The tissue section of diseased muscle tissue shows “white holes,” which represent
unstained aggregates of glycogen particles. Glycogen accumulation interferes with muscle cell
function and contraction, and heart failure—a heavily impacted, severely distended heart is
shown here in an X-ray image—leads to death.
The condition, which is known as Pompe’s disease, can vary in severity; complete lack of
enzyme activity becomes manifest in infants, whereas mutations that reduce but do not
completely inactivate the enzyme will cause milder disease with onset deferred to later childhood
or adolescence. The disease can be treated with enzyme replacement therapy. The recombinant
enzyme preparation is FDA-approved; its price is astronomical. Muscle phosphorylase
deficiency (McArdle’s disease)
•Deficient glycogen breakdown inhibits rapid ATP replenishment
•Patients experience rapid exhaustion and muscle pain during exertion
•Liver phosphorylase and blood glucose homeostasis remain intact
Notes: Since liver and muscle phosphorylase are distinct isozymes, defects usually affect one and
spare the other. In McArdle’s disease, the muscle isoform that is selectively affected. An
unexplained symptom in this disease is the so-called “second wind” phenomenon: during
physical activity, patients initially fatigue rapidly, but then recover to a degree under continued
exercise.
The lack of muscle phosphorylase should also inhibit the utilization of muscle glycogen toward
blood glucose stabilization by way of the Cori cycle; one might therefore expect that McArdle’s
disease might involve episodes of hypoglycemia. Interestingly, however, the literature does not
contain reports of hypoglycemia in these patients.
Lafora disease
•Deficiency for laforin, a glycogen phosphatase
•Accumulation of hyper-phosphorylated glycogen (Lafora bodies)
•Patients develop epilepsy, dementia
Notes: Laforin is a phosphatase that is associated with glycogen particles and removes phosphate
groups from glycogen itself. The functional significance of glycogen phosphorylation and
dephosphorylation is not clear; and you will notice that it was not even mentioned above.
However, genetic deficiencies of the phosphatase lead to the accumulation of Lafora bodies,
which consist of phosphorylated, poorly branched glycogen molecules. The disease becomes
manifest through a specific form of epilepsy (myoclonic seizures) and dementia and is fatal. The
CNS symptoms— like the involvement of the kidneys in v. Gierke disease, see above—illustrate
that tissues other than liver and muscle contain glycogen as well and may be damaged by its
accumulation.
THE HEXOSE MONOPHOSPHATE SHUNT
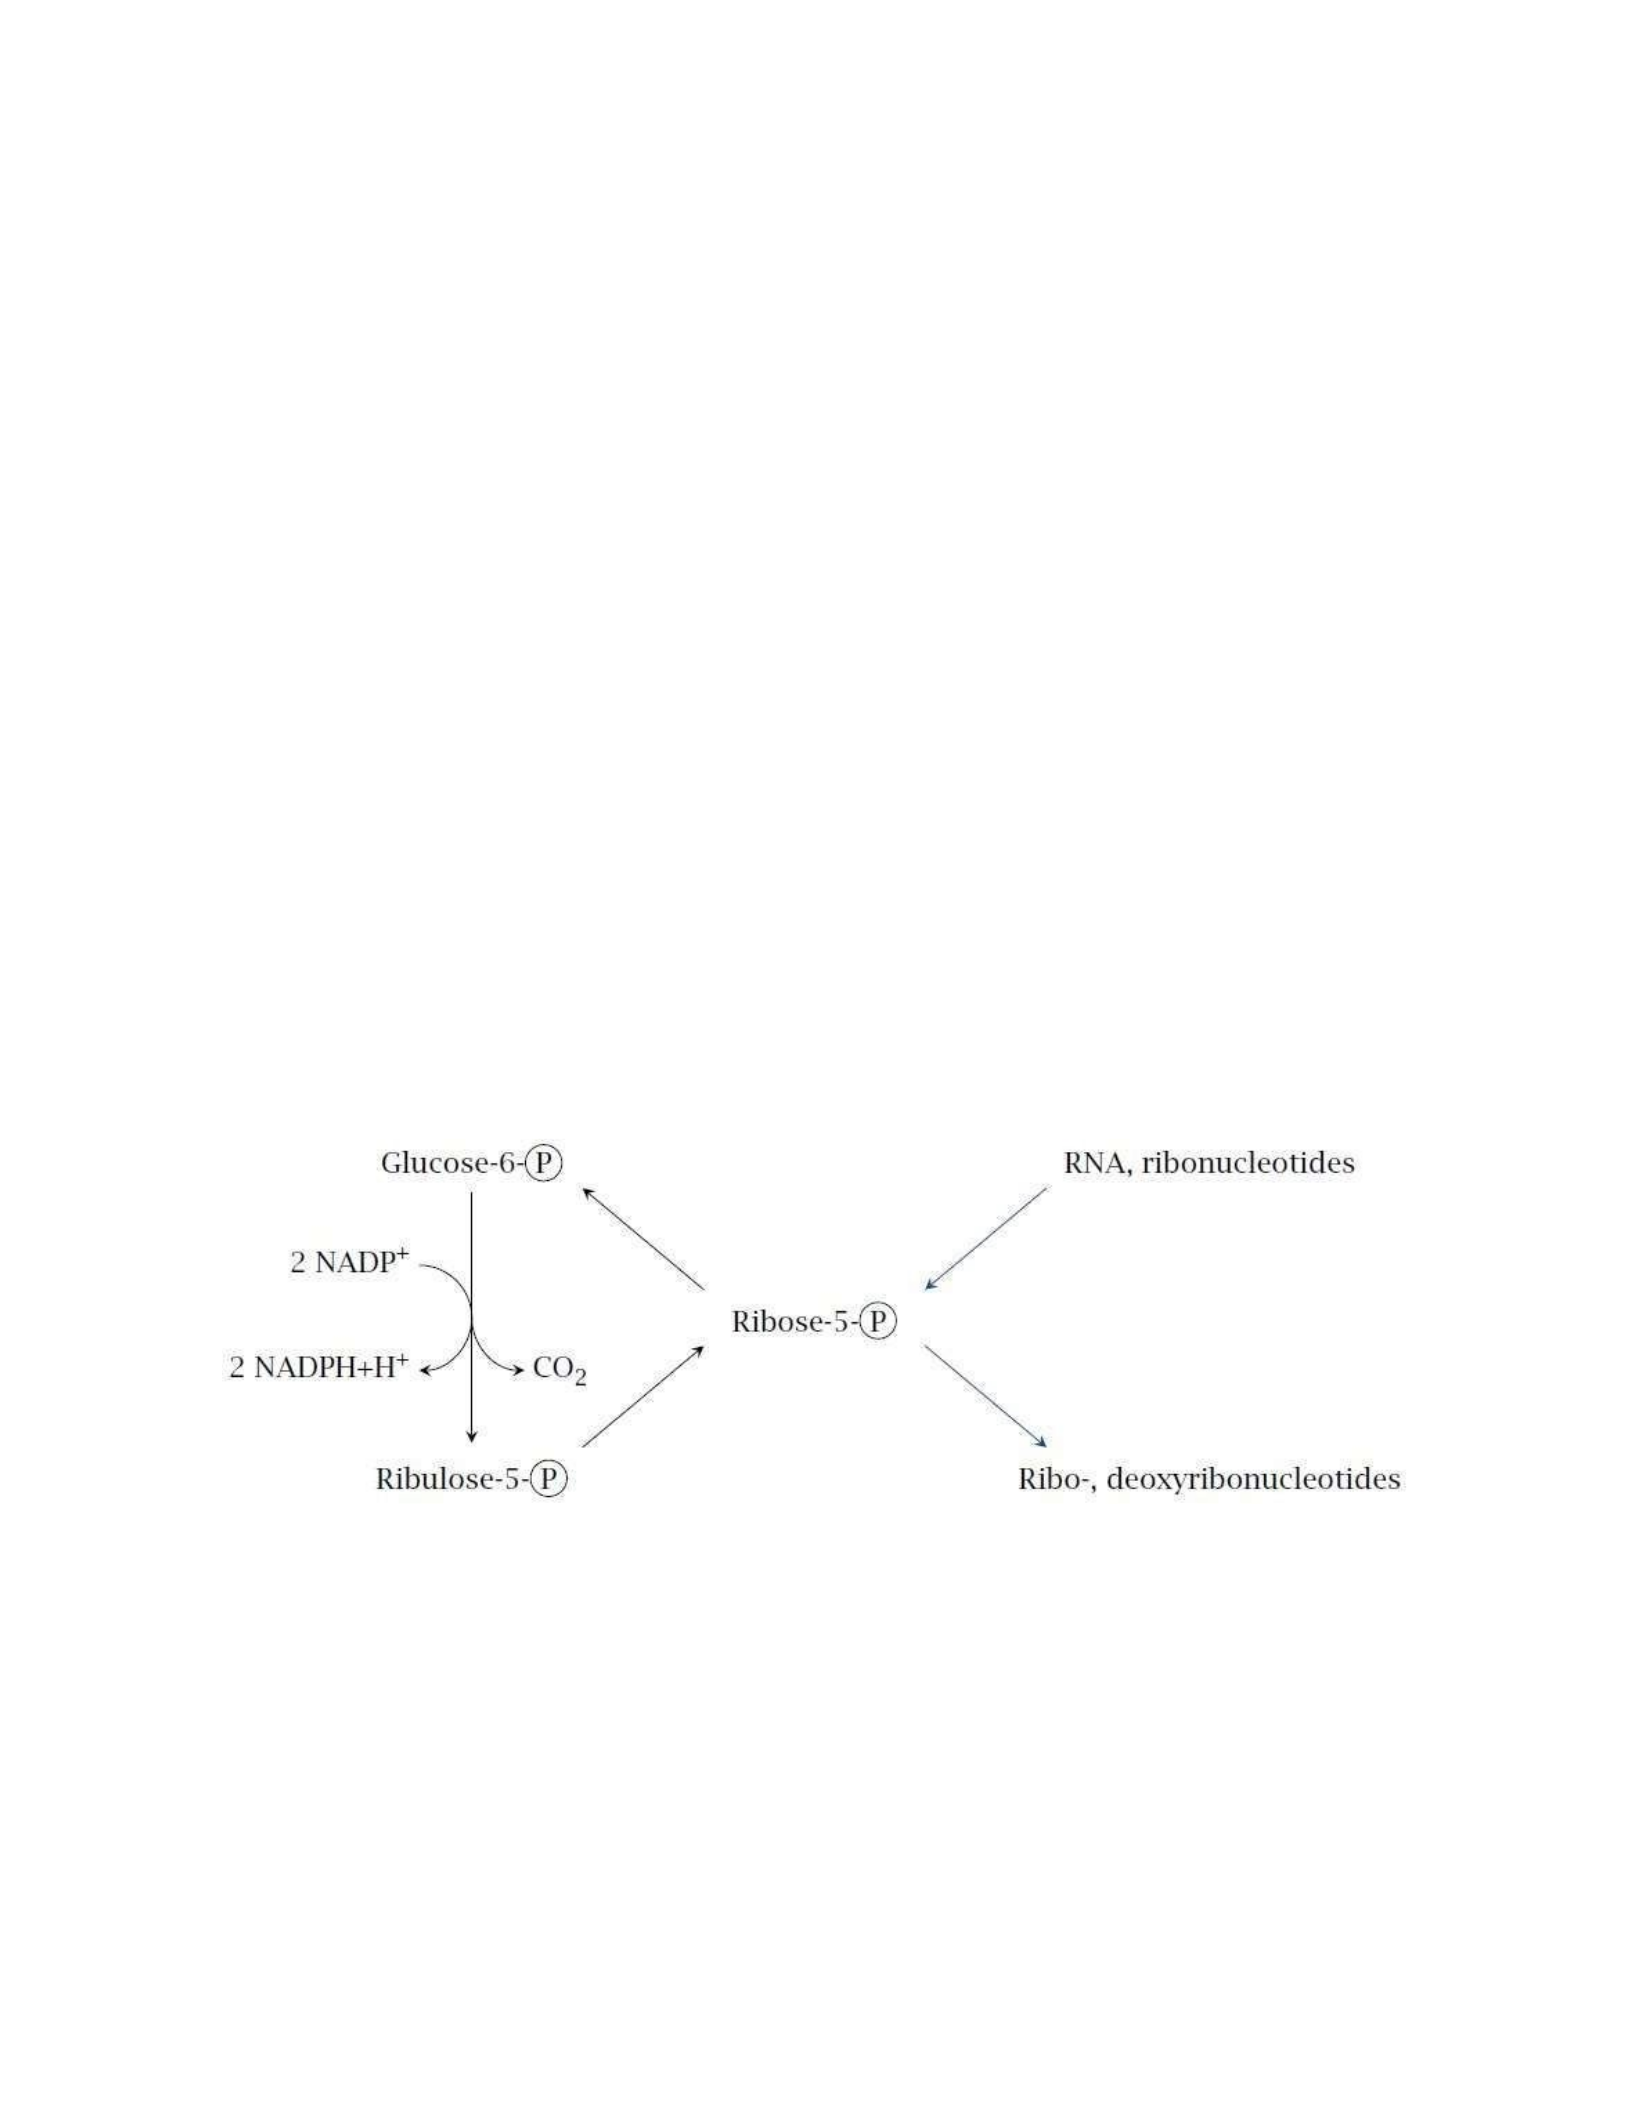
Outline of the pathway
Notes: The previous topics have shown that glucose-6-phosphate has a central place in
carbohydrate metabolism. This topic describes yet another pathway that starts with this key
metabolite, namely the hexose monophosphate shunt, or HMS for short. Since this pathway
comprises both pentoses and hexoses, it is sometimes also referred to as the pentose phosphate
pathway. It serves two major functions that are important for biosynthesis, namely (1) the
generation of reduced NADPH, and (2) the provision or utilization of ribose. Within the pathway,
we can distinguish two major phases:
1. the oxidative phase, in which glucose-6-phosphate is oxidized and decarboxylated to
ribulose- 5-phosphate, and which yields two equivalents of NADPH, and
2. the regenerative “sugar shuffle” phase, which converts ribulose-5-phosphate back to 5/6
equivalents of glucose-6-phosphate.
If all the glucose-6-phosphate formed in the regenerative phase reenters the oxidative phase in
each turn of the cycle, all of it will eventually be completely oxidized to CO2, with the
production of 12 equivalents of NADPH. Therefore, the hexose monophosphate shunt provides
an alternate pathway for the complete degradation of glucose to CO2. While the sequence of
glycolysis, PDH and TCA involves both the cytosol and the mitochondria, the HMS runs entirely
in the cytosol. This ties in with the fact that most of the biosynthetic reactions that require
NADPH also occur in the cytoplasm or in the ER, rather than in the mitochondria. It also means
that the HMS is present in red blood cells, which lack mitochondria.
The oxidative and the regenerative phases of the HMS can occur at the same time, but they can
also function independently from one another. This allows net flux through the pathway to
follow alternative patterns in different metabolic situations:
1. NADPH regeneration. Complete oxidation of glucose-6-phosphate, with maximum
yield of NADPH and without any net formation or utilization of other sugars, occurs when the
oxidative phase and the regenerative phase occur in lockstep.
2. Nucleotide biosynthesis. One of the sugar phosphate intermediates of the regenerative
phase is ribose-5-phosphate, which also serves as a precursor of nucleotides and nucleic acids. If
required, ribose-5-phosphate can be diverted toward nucleotide biosynthesis, with a
corresponding reduction in the yield of regenerated glucose-6-phosphate. Since all reactions in
the regenerative phase are reversible, glucose-6-phosphate can in principle also be converted to
ribose-5-phosphate without any concomitant net oxidation.
3. Ribose utilization. With a typical diet that is reasonably rich in starch, the net flow
through the sugar shuffle will be from hexoses to pentoses. However, when eating meat only, our
intake of ribose in the form of RNA will be a very significant fraction of the total dietary
carbohydrates, and the net flow in the hexose monophosphate shunt will likely go the opposite
way.
Reactions in the hexose monophosphate shunt
Reactions in the oxidative stage
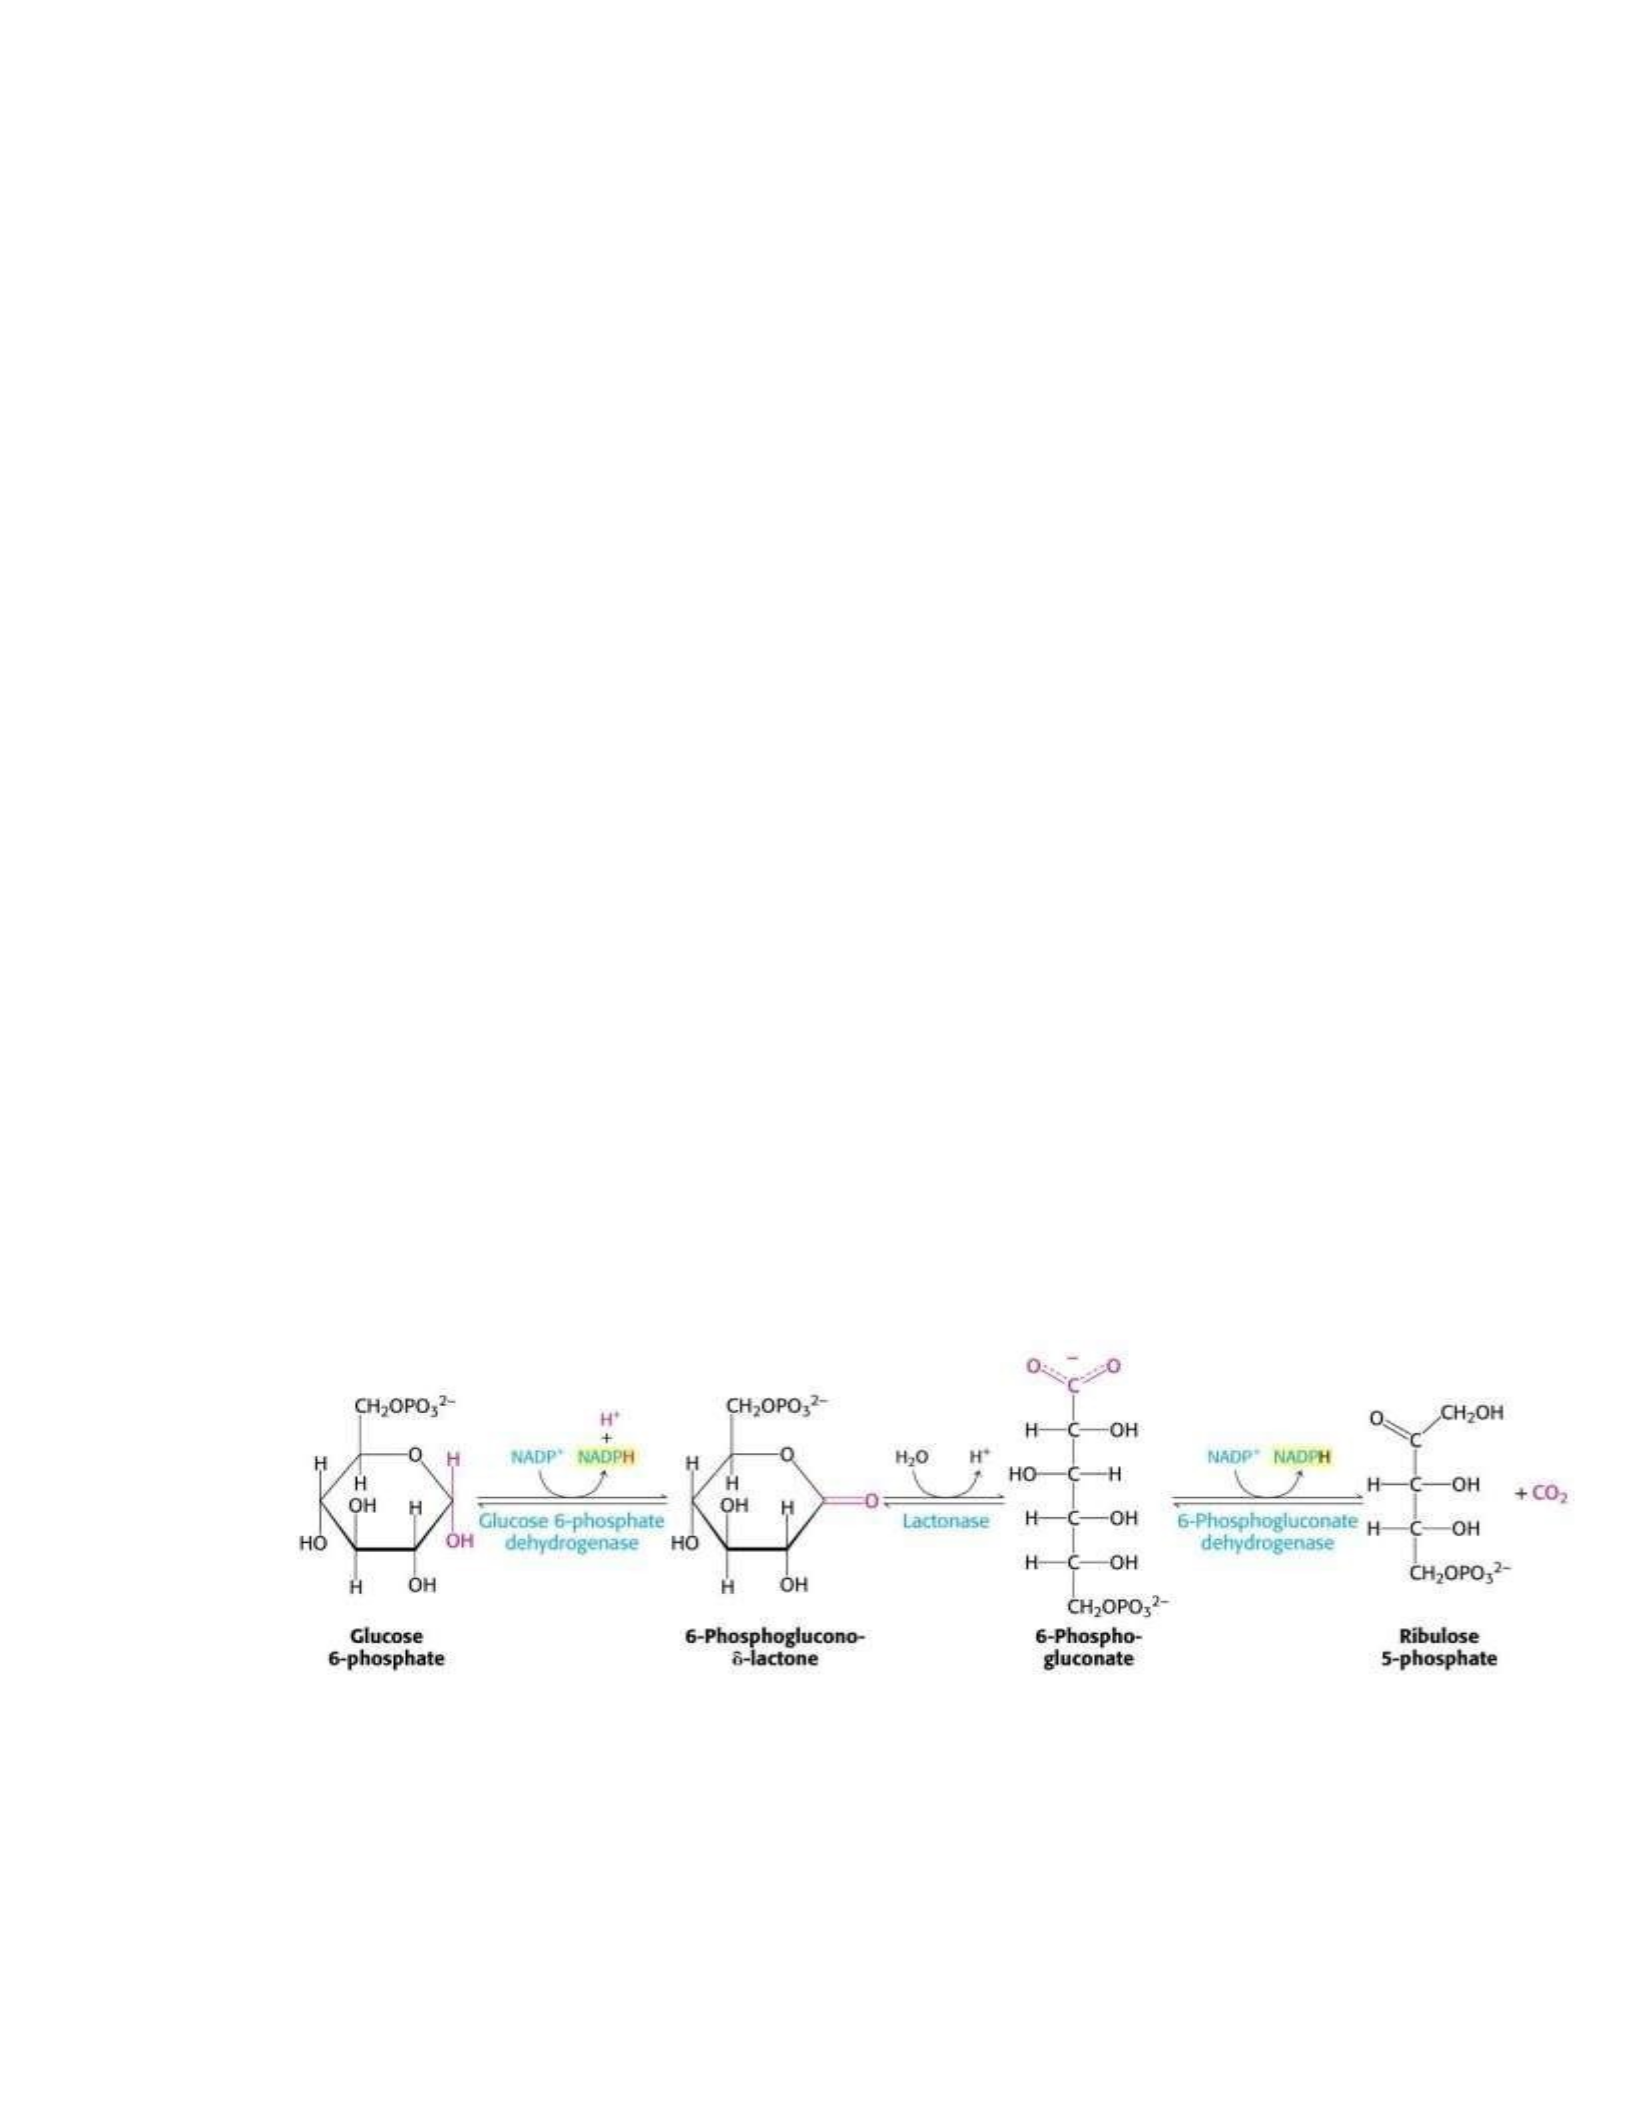
Notes: Three enzymes are required in the oxidative phase:
1. Glucose-6-phosphate dehydrogenase oxidizes glucose-6-phosphate to
6phosphogluconolactone and reduces one molecule of NADP+ to NADPH.
2. Gluconolactonase cleaves the internal ester bond and produces 6-phosphogluconate.
3. 6-Phosphogluconate dehydrogenase reduces another molecule of NADP+ and decarboxylates
6-phosphogluconate to the pentose ribulose-5-phosphate.
After completion of these three initial reactions, NADPH generation is over, and all that remains
is to juggle sugars in order to regenerate hexoses from pentoses.
Reactions in the sugar shuffle stage
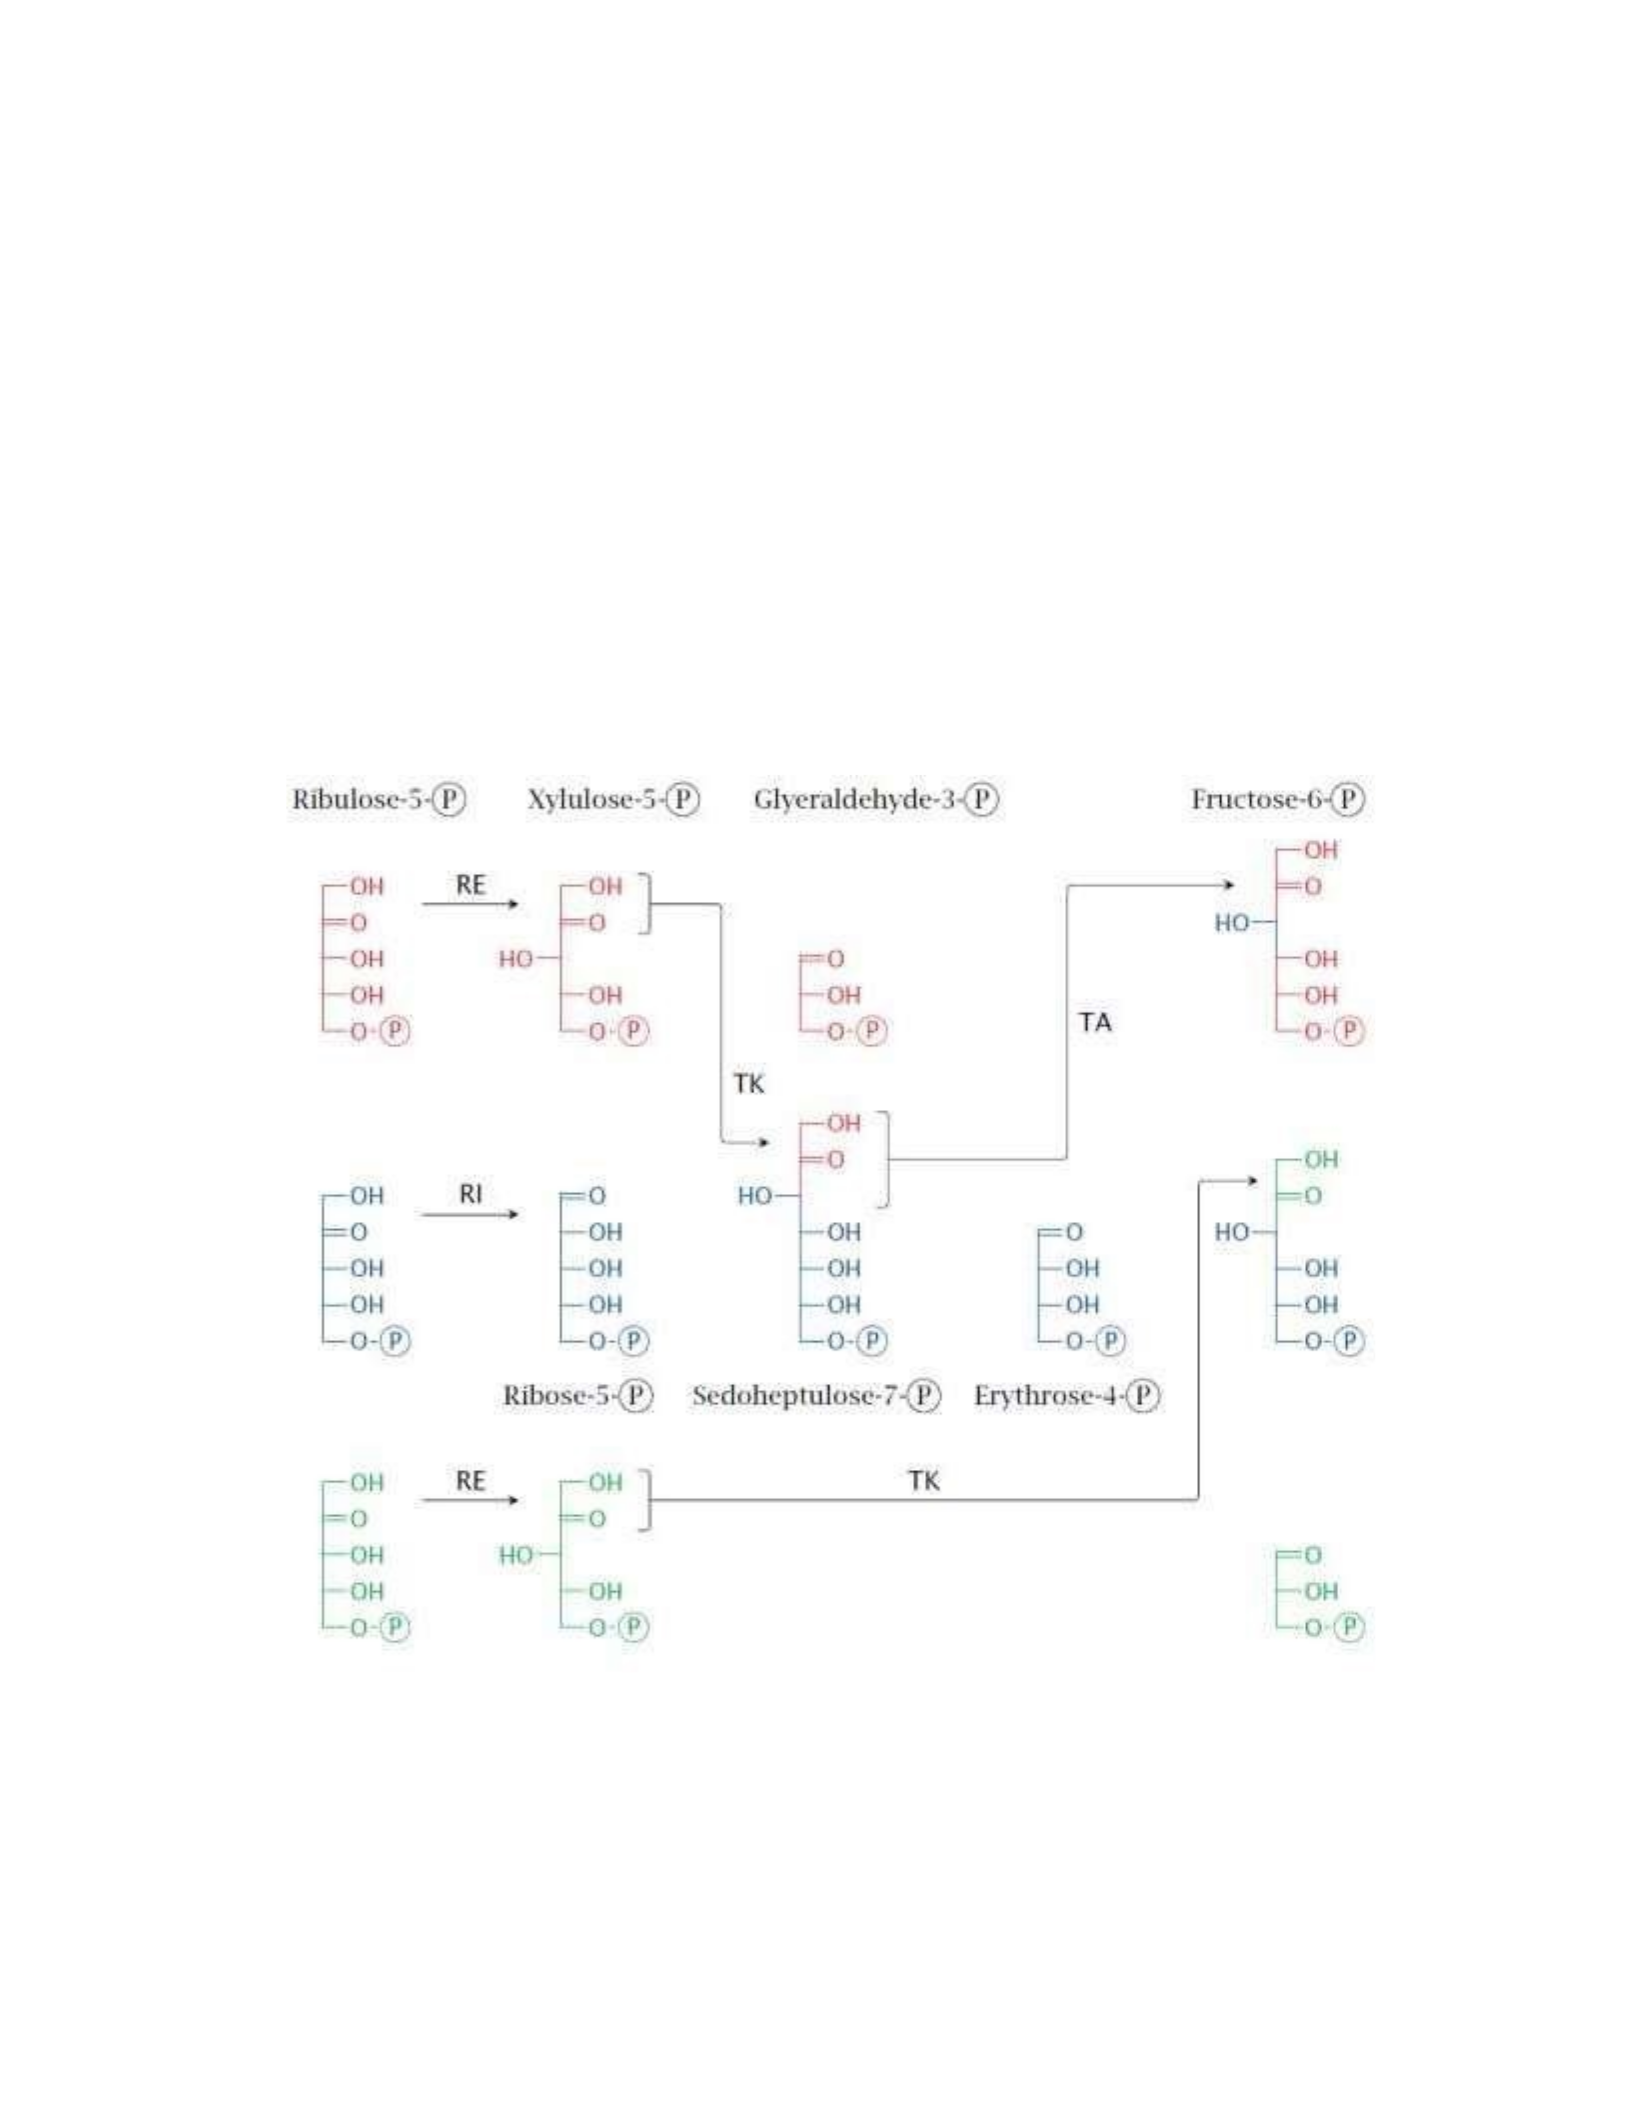
These reactions are by two special enzymes; transketolase and transaldolases.
Transketolase catalyzes the transfer of two-carbon fragment from a ketose donor to an
aldose acceptor. In its first appearance in the pentose phosphate pathway, transketolase
transfers C-1 and C-2 of xylulose 5- phosphate to ribose-5-phosphate, forming the
seven- carbon product, sedoheptulose 7-phosphate. The remaining three-carbon
fragment from xylulose is glyceraldehyde-3-phosphate.
Transaldolase catalyzes a reaction similar to the aldolase reaction of glycolysis: a three-carbon
fragment is removed from sedoheptulose 7-phosphate and condensed with glyceraldehyde
3phosphate, forming fructose 6- phosphate and the tetrose erythrose-4-phosphate. Now
transketolase acts again, forming fructose 6-phosphate and glyceraldehyde-3-phosphate from
erythrose 4phosphate and xylulose 5-phosphate.
Notes: The sugar shuffle stage involves the enzymes ribulose-5-phosphate epimerase (RE),
ribulose-5-phosphate isomerase (RI), transketolase (TK), and transaldolase (TA).
They bring about the following reactions:
1. Two molecules of ribulose-5-phosphate are converted to xylulose-5- phosphate by
ribulose-5- phosphate epimerase, and a third one is converted to ribose-5-phosphate by ribulose-
5-phosphate isomerase.

2. Transketolase transfers a C2 unit from one xylulose-5-phosphate to the ribose-5-
phosphate, yielding glyceraldehyde-3-phosphate and the C7 sugar sedoheptulose-7- phosphate.
3. Transaldolase transfers a C3 unit from sedoheptulose-7-phosphate back to
glyceraldehyde-3 phosphate, which yields fructose-6-phosphate and the C4 sugar erythrose- 4-
phosphate.
4. Transketolase transfers a C2 unit from the second molecule of xylulose-5-phosphate to
erythrose-4-phosphate. This yields a second molecule of fructose-6-phosphate and again
glyceraldehyde-3-phosphate. At the conclusion of the reactions depicted in this slide, three
molecules of ribulose-
5-phosphate have been converted to two molecules of fructose-6-phosphate and one molecule of
glyceraldehyde-3-phosphate. Fructose-6-phosphate can be converted to glucose-6-phosphate in
one step by phosphohexose isomerase, a glycolytic enzyme.
Conversion of glyceraldehyde-3-phosphate to glucose-6-phosphate would require several
enzymes from glycolysis as well as fructose-1,6-bisphosphatase, which otherwise is only
required in gluconeogenesis. I have not been able to ascertain whether or not tissues that don’t
perform gluconeogenesis produce this enzyme to serve in the hexose monophosphate shunt. Also
recall that two molecules of triose phosphate are needed in the aldolase reaction to form one
molecule of fructose-1,6-bisphosphate. This results in an overall stoichiometry of 2.5 molecules
of hexose per 3 molecules of pentose, or five hexoses per six pentoses.
Notes: The shuffling of sugars differing in chain length is brought about by just two enzymes,
namely transaldolase and transketolase. While the sugar substrates they act upon may appear to
be quite varied at first glance, they fall into just two homologous classes, within each of which
the members differ only in the number of CHOH groups in their “tails”. The two enzymes only
interact with the “head” parts of each of these sugar molecules, so that the chain length of the
remainder doesn’t enter into the picture and does not create a need for separate enzyme
specificity.
The basic idea of chain length variation is that transketolase always transfers two carbon units,
whereas transaldolase always transfers three-carbon units.
The physiological role of NADPH
Our discussion of the HMS pathway is now concluded, and we will now have a look at the
various metabolic functions of NADPH.
Why do we need both NADH and NADPH?
Notes: Why is NADPH needed in addition to NADH? The two coenzymes only differ by one
phosphate group, and that group is far away from where the action is: The redoxactive group is
the pyridine ring in the nicotinamide moiety (highlighted), whereas the extra phosphate in NADP
is located on the adenosine moiety at the other end of the molecule.
While the phosphate group does not make any difference to the redox chemistry performed by
the two coenzymes, it enables them to interact with separate sets of enzymes. Consider that all
enzymes that consume or regenerate NAD+ will share the same pool of the coenzyme, and the
reaction equilibria of all of them will be affected by the same ratio of oxidized to reduced form,
[NAD+]/[NADH].

The extra phosphate group on NADP allows it to interact with another, different set of enzymes.
Therefore, because the coenzymes participate in separate sets of equilibria, they can themselves
be maintained in different redox states. To use a simile: the two coenzymes are like two different
currencies—both are money, but it is possible to tune the cost of borrowing of each separately to
different economic objectives. Inside the cell, NAD is mostly oxidized. The ready availability of
NAD+ will help to speed up the oxidative reactions in the TCA and glycolysis. In contrast,
NADP is mainly found in the reduced state, which will promote reductive reactions in
biosynthesis.
Uses of NADPH
1. Synthesis of fatty acids and cholesterol
2. Fixation of ammonia by glutamate dehydrogenase
3. Oxidative metabolism of drugs and poisons by cytochrome P450 enzymes
4. Generation of nitric oxide and of reactive oxygen species by phagocytes
5. Scavenging of reactive oxygen species that form as byproducts of oxygen transport and of the
respiratory chain
Glucose-6-phosphate dehydrogenase deficiency
•X-chromosomally encoded—males more severely affected
•Most patients are healthy most of the time—hemolytic crises occur upon exposure to drugs or
diet components that cause enhanced formation of ROS
•Manifest in red blood cells because these cells lack protein synthesis—no replacement of
deficient protein molecules
•Affords partial protection against malaria—similar to sickle cell anemia and other
hemoglobinopathias
Notes: Red blood cells lack mitochondria and thus depend entirely on the HMS for NADPH
regeneration. Mutations in glucose-6-phosphate dehydrogenase (the first enzyme in the pathway)
that reduce its activity limit the supply of NADPH and, therefore, the capacity of the cell to
detoxify reactive oxygen species. ROS that go un-scavenged will cause the peroxidation of
membrane lipids and destroy the cell. This condition—namely, the occurrence of episodes of
hemolytic anemia upon ingestion of ROS-inducing foods or drugs—is called favism.
Glucose-6-phosphate dehydrogenase is encoded on the X chromosome, and accordingly males
(who have only one X chromosome) are affected the most. However, heterozygous females are
not exempt, since, in keeping with the “Mary Lyon hypothesis,” one of the two X chromosomes
in females is inactivated randomly early during embryonic development, and therefore, in
heterozygote females, the bone marrow precursors of the red blood cells will represent a mosaic
of intact and deficient genes. Indeed, the observation of such a mosaic in glucose-6-phosphate
dehydrogenase deficiency was the first proof of random X chromosome inactivation in humans.
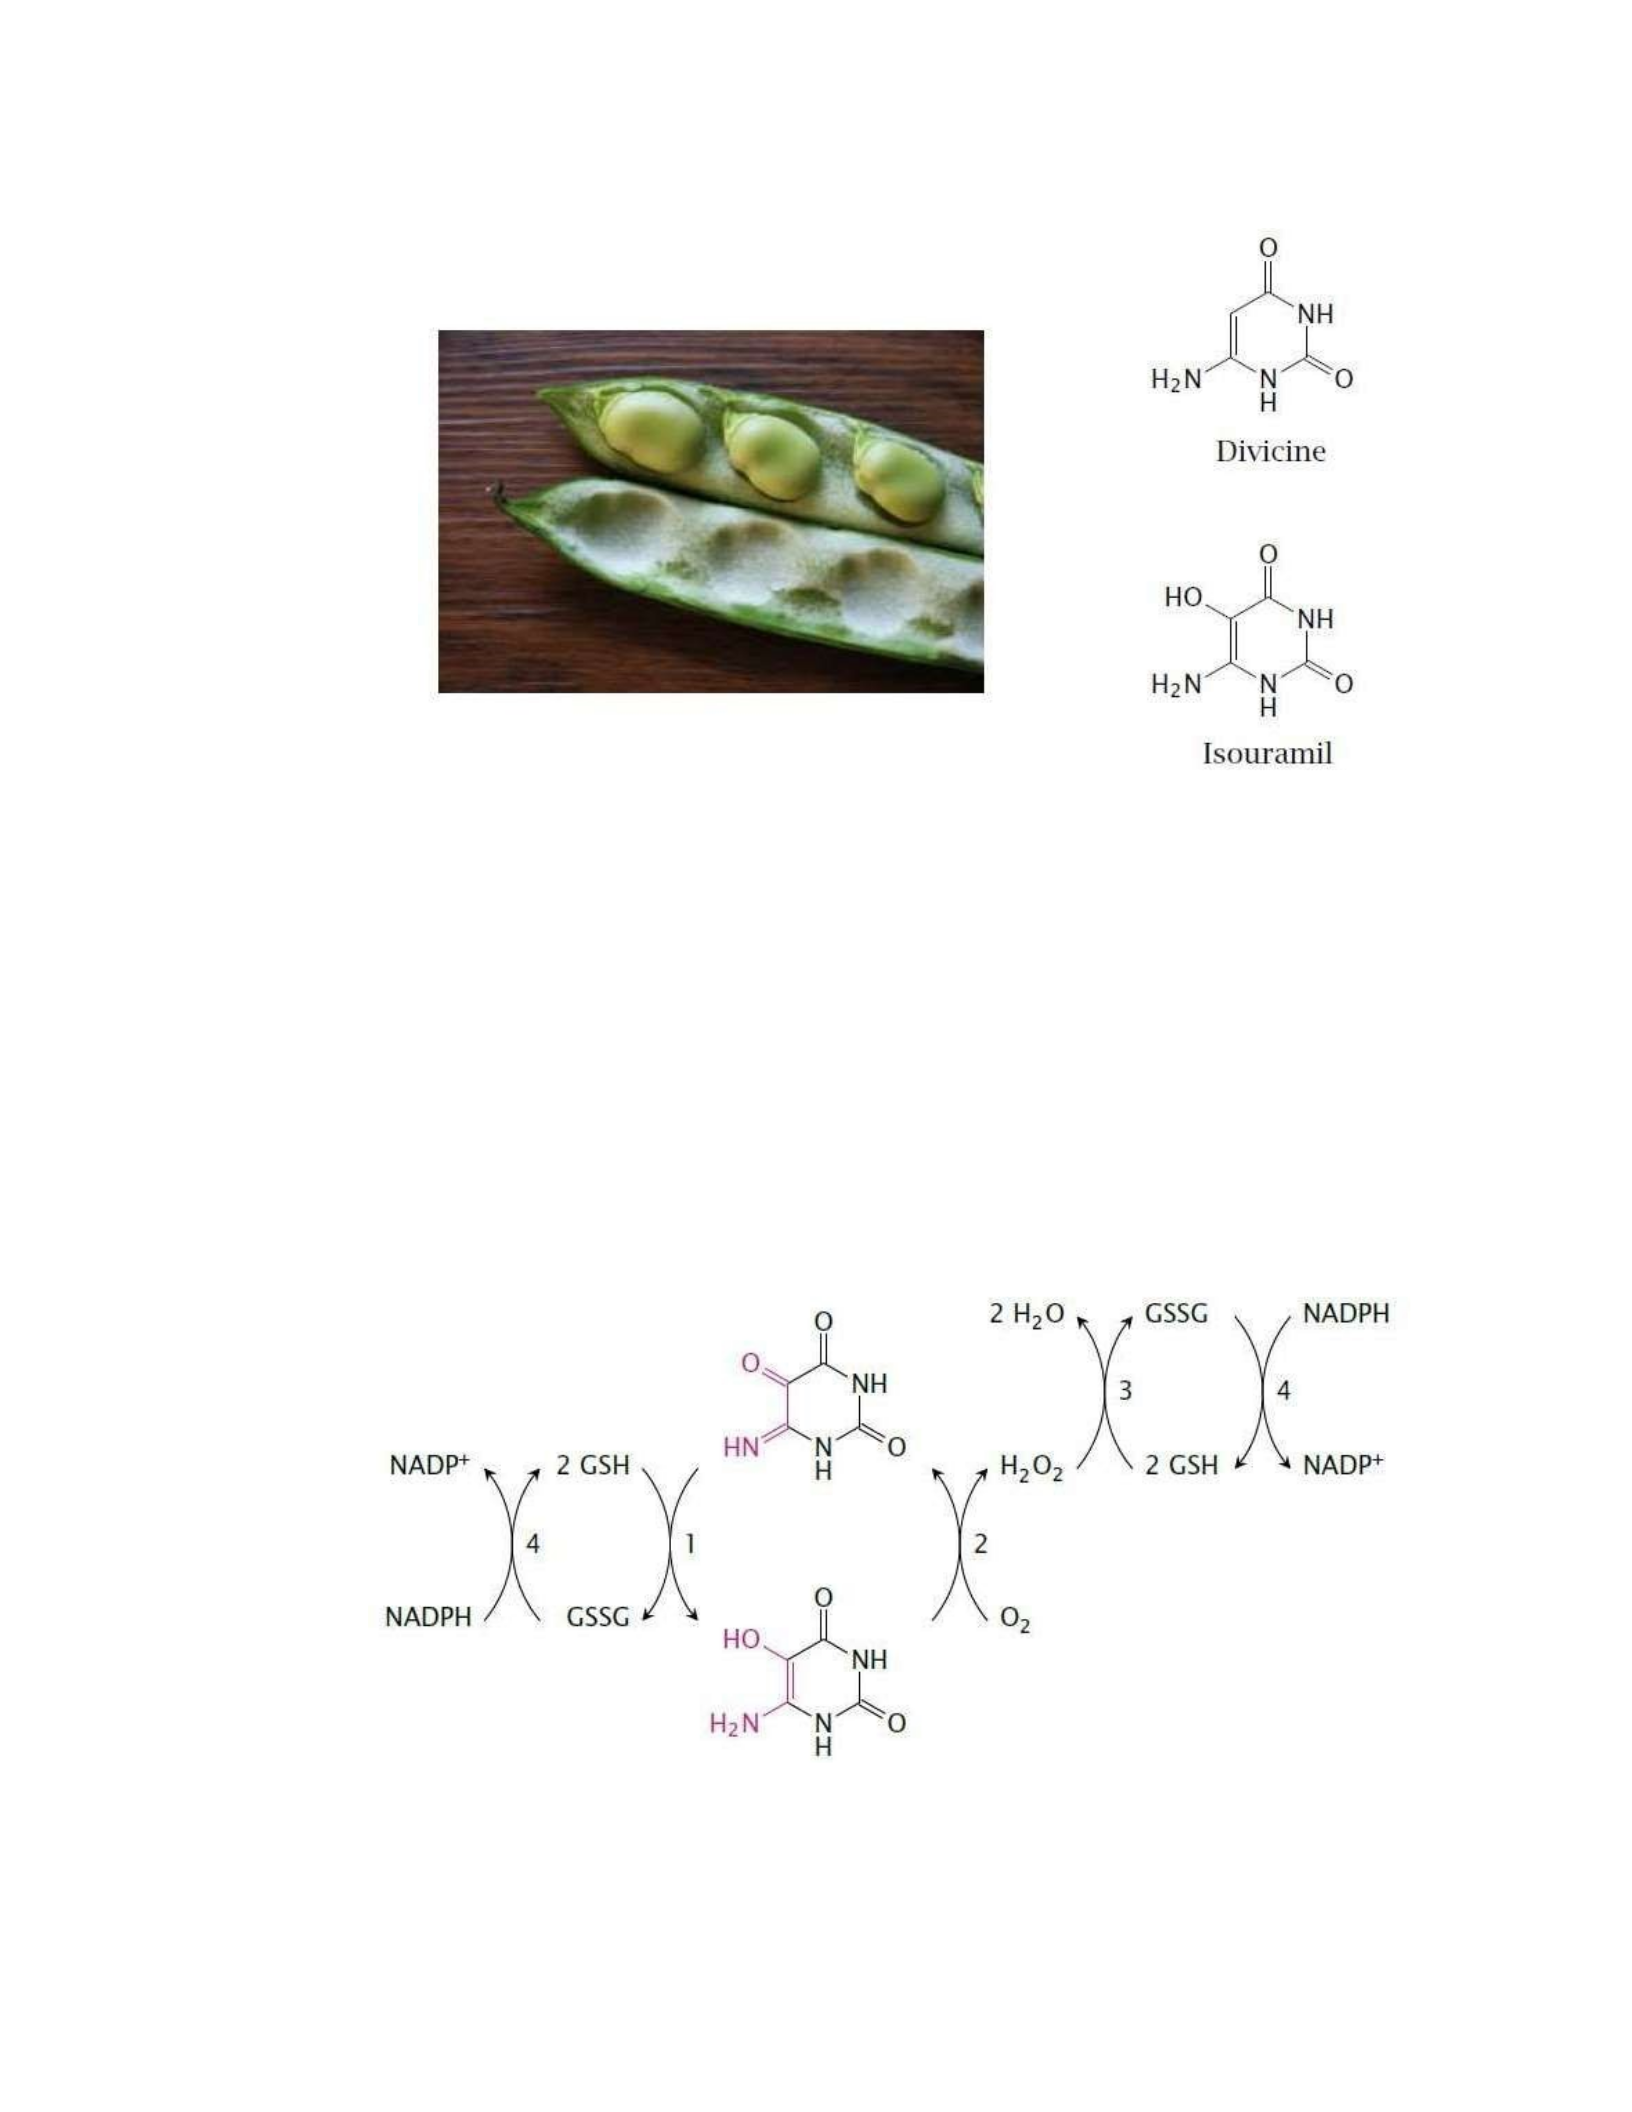
Vicia faba and favism
Notes: The name “favism” derives from that of the broad bean, Vicia faba, which contains
several ingredients including isouramil and divicine that can trigger hemolytic crises. The strong
induction of ROS by these compounds is due to redox cycling.
Redox cycling of isouramil
Notes: This scheme outlines the redox cycle induced by isouramil. Reactions (1) and (2) occur
spontaneously, without any need for enzymatic catalysis. The H2O2 formed in reaction (2) is
reduced by glutathione peroxidase (3). The glutathione disulfide formed in reactions (1) and (3)
is reduced at the expense of NADPH in reaction (4) by glutathione reductase. Therefore, this
redox cycle that consumes four equivalents of reduced glutathione (GSH) in every full turn.
Divicine and some other substances contained in broad beans cause analogous cycles.
Wernicke-Korsakoff Syndrome Is Exacerbated by a Defect in Transketolase in the pentose
phosphate pathway
Wernicke-Korsakoff syndrome is a disorder caused by a severe deficiency of thiamine, a
component of TPP. The syndrome is more common among people with alcoholism than in the
general population, because chronic, heavy alcohol consumption interferes with the intestinal

absorption of thiamine. The syndrome can be exacerbated by a mutation in the gene for
transketolase that results in an enzyme with a lowered affinity for TPP—an affinity one-tenth that
of the normal enzyme. This defect makes individuals much more sensitive to a thiamine
deficiency: even a moderate thiamine deficiency (tolerable in individuals with an unmutated
transketolase) can drop the level of TPP below that needed to saturate the enzyme. The result is a
slowing down of the whole pentose phosphate pathway. In people with Wernicke-Korsakoff
syndrome this results in a worsening of symptoms, which can include severe memory loss, mental
confusion, and partial paralysis.
GLUCOSE METABOLISM REGULATION
The metabolism of glucose is highly regulated. Control of the pathways is mainly at enzymes controlling the
irreversible and committed steps of the specific pathway. The regulation is either by allosteric effectors or by
phosphorylation. Allosteric effectors are molecules which bind at the allosteric site of the enzyme (a site
different from the active site) and either activate or inhibit the enzyme. Allosteric effectors include:
1. End products of a step (feedback inhibition)
2. Substrates of the pathway (feed forward activation)
3. Indicators of energy status of the cell which include ATP, AMP, Acetyl CoA etc. This either activate
or inhibit the said enzyme depending on the role of the pathway.
GLYCOLYSIS REGULATION
The Glycolytic Pathway Is Tightly Controlled
The glycolytic pathway has a dual role: it degrades glucose to generate ATP, and it
provides building blocks for the synthesis of cellular components. The rate of conversion
of glucose into pyruvate is regulated to meet these two major cellular needs. Under
physiological conditions, the reactions of glycolysis are readily reversible except for those
catalyzed by hexokinase, phosphofructokinase, and pyruvate kinase.
Phosphofructokinase, the most important control element in glycolysis, is inhibited by high
levels of ATP and citrate, and it is activated by AMP and fructose 2,6-bisphosphate. In the
liver, this bisphosphate signals that glucose is abundant. Hence, phosphofructokinase is
active when either energy or building blocks are needed. Hexokinase is inhibited by
glucose 6-phosphate, which accumulates when phosphofructokinase is inactive. ATP and
alanine allosterically inhibit pyruvate kinase, the other control site, and fructose 1,6-
bisphosphate
activates the enzyme. Consequently, pyruvate kinase is maximally active when the energy charge
is low and glycolytic intermediates accumulate.
GLYCOGEN METABOLISM
Both synthesis and breakdown of glycogen are spontaneous. If both pathways are active
simultaneously in a cell, there would be a futile cycle. Hence, the key enzymes glycogen synthase
and glycogen phosphorylase are reciprocally regulated by allosteric effectors and by
phosphorylation.
In regulation by allosteric effectors, glycogen phosphorylase is activated by high amounts of AMP and
inorganic phosphate (Pi) while its inhibited by high amount of ATP and Glucose -6 – phosphate.
On the other hand, Glycogen synthase is allosterically activated by Glucose -6- phosphate
Regulation by covalent modification – the hormones glucagon and epinephrine activates G- protein
coupled receptors leading to formation of Camp and in response activating the glycogen
phosphorylase and inhibit glycogen synthase. Ultimately, this leads to activation of glycogen
breakdown.
In the liver, this activation is by glucagon with the sole aim of increasing blood sugar while in the
muscles, this activation is by epinephrine leading to energy production.
Insulin, produced in response to high blood glucose triggers a separate signal cascade that leads to
activation of phospoprotein kinase and ultimately activates glycogen synthase antagonizing the
effect of glucagon and epinephrine
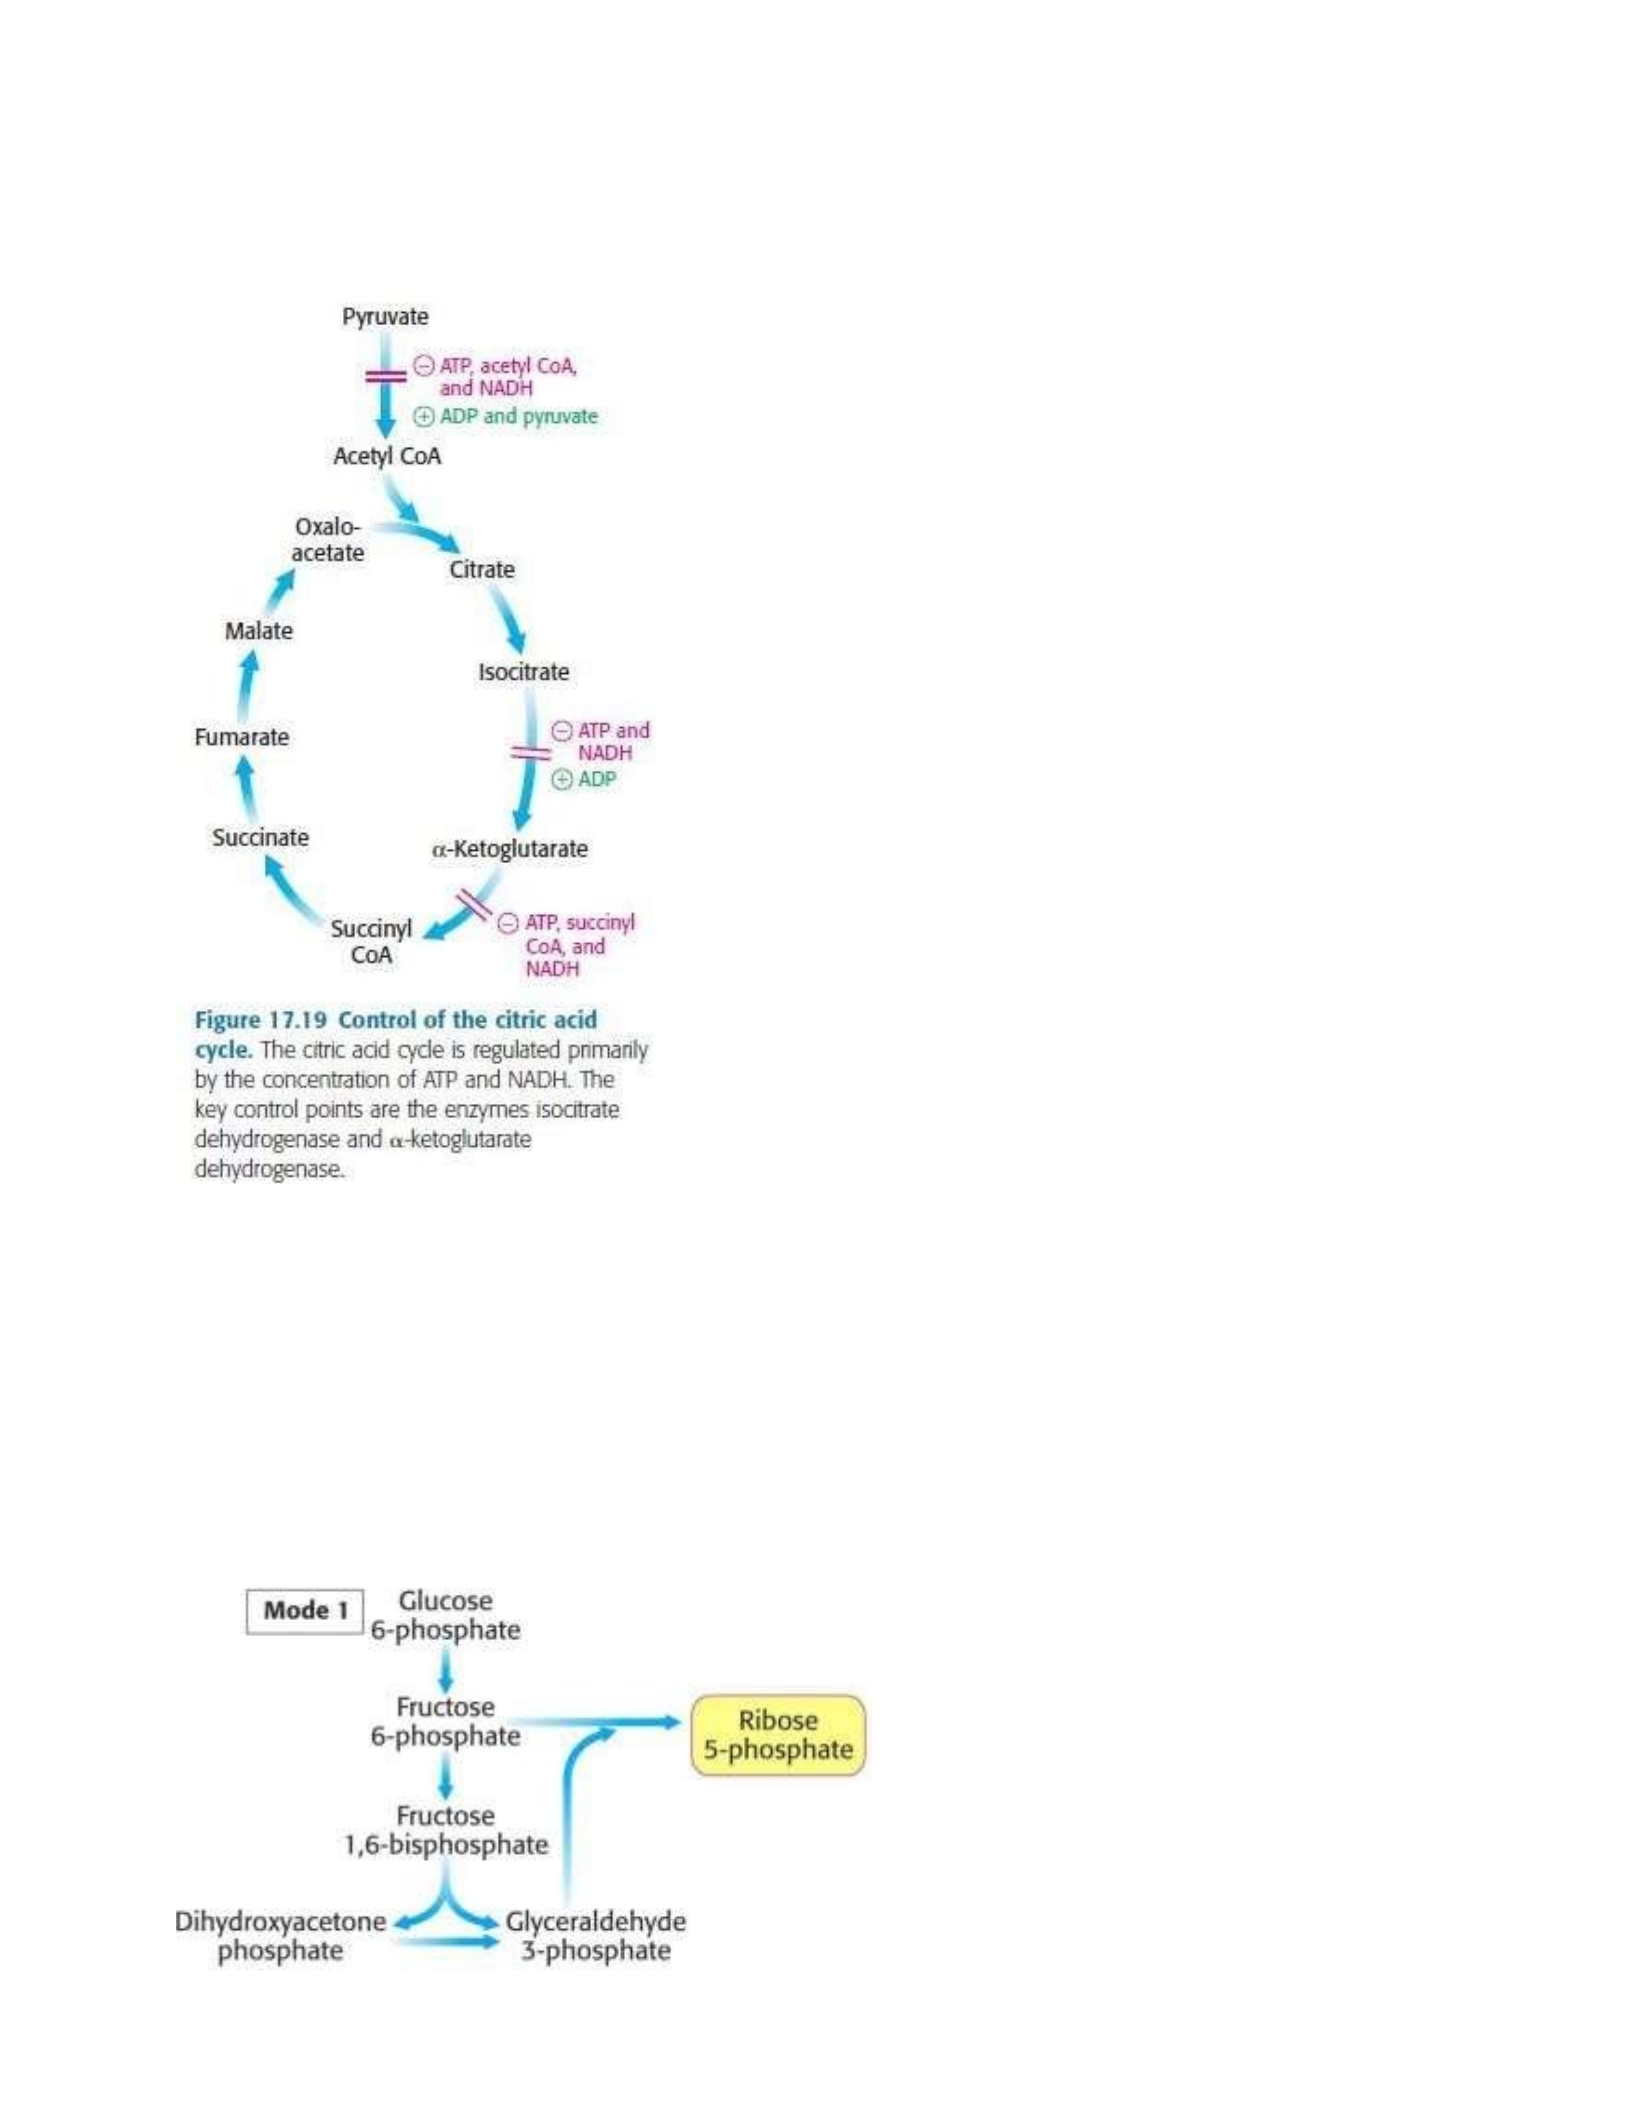
TCA cycle
Pentose phosphate pathway
Glucose -6 phosphate Dehydrogenase enzyme is the regulatory enzyme. It is inhibited by NADPH
by feedback inhibition. Usually high ratio of NADPH/NADP+ inhibits the enzyme but with
increased demand for NADPH, the ratio decreases and the enzyme activity is stimulated.
The reactions of the non – oxidative portion of the pentose pathway are readily reversible. The
concentrations of the products and reactants can shift depending on the metabolic needs of a particular cell
or tissue.
1. For instance in rapidly diving cell, high ribose 5- phosphate is required
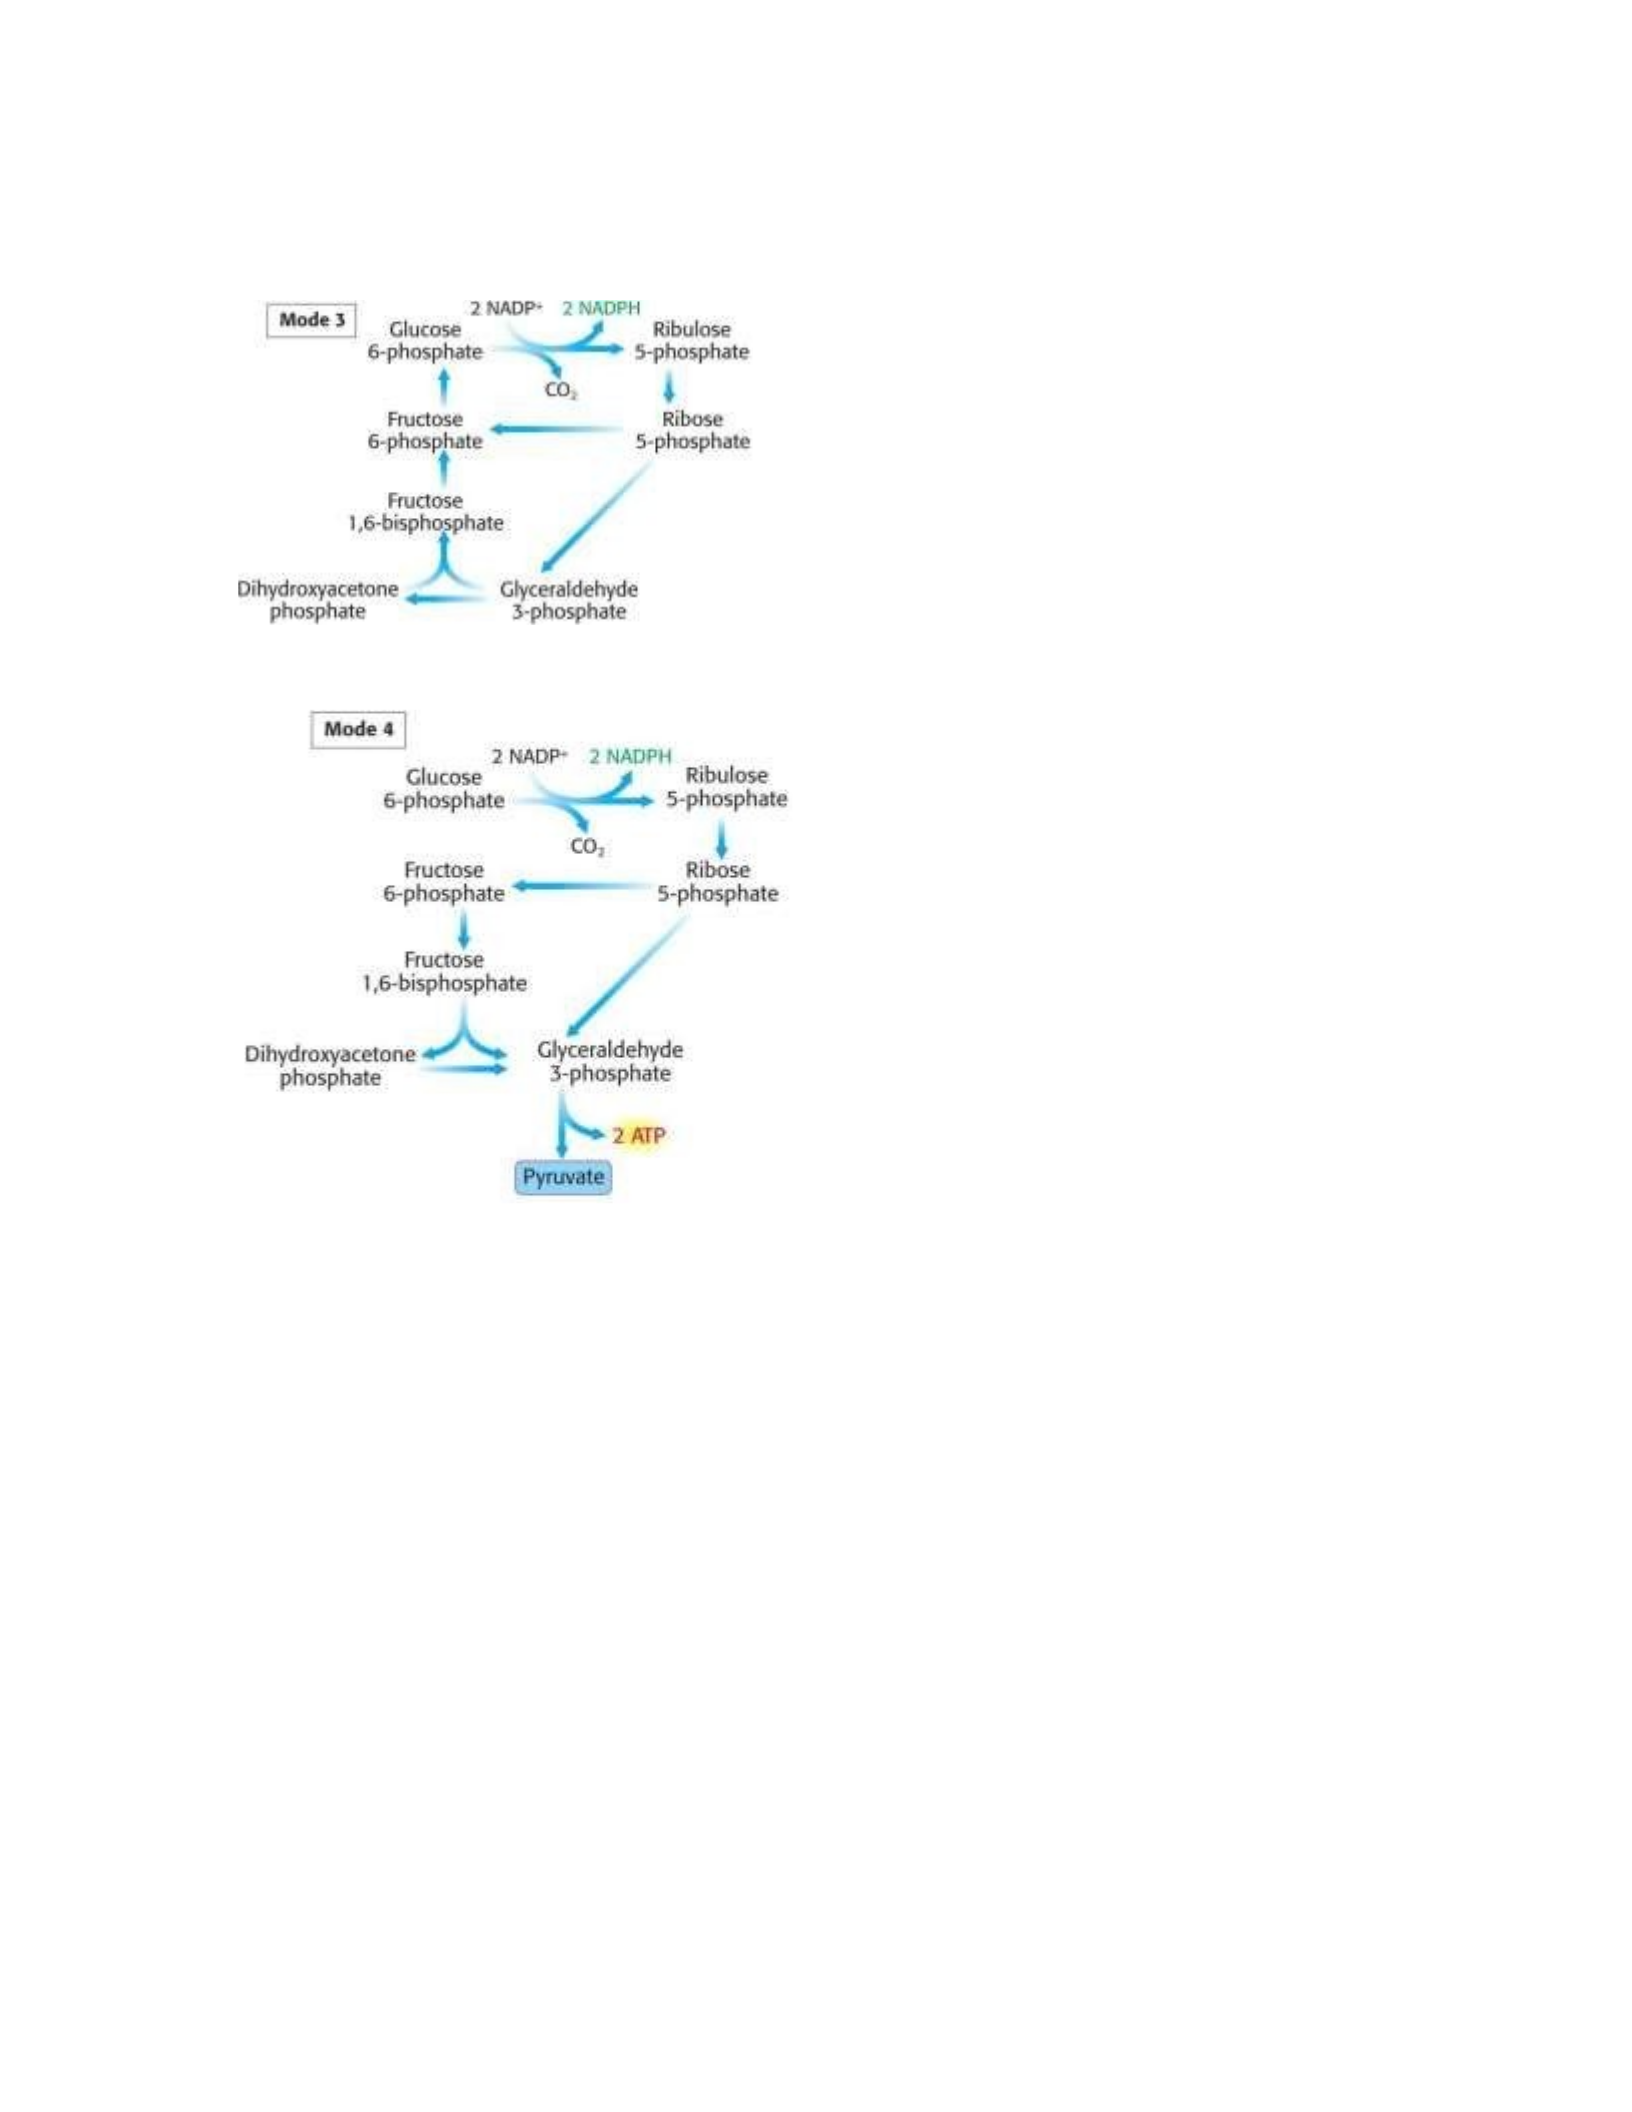
2. When more NADPH is needed than ribose 5- phosphate (eg during fatty acid synthesis and
detoxification
3. When the cell needs both NADPH and ATP

