


Gaucher Disease – A Sphingoliposis
1. What are sphingolipids and why are they physiologically important? Give particular examples...
Glycolipids=glycosphingolipids-sphingolipids are made of carbs and lipid components. They are found mostly
in nerve tissues in the outer leaflet, so they interact with the extracellular environment. They play a role in
regulation of cellular interactions, growth, and development. Membrane glycolipids associate with cholesterol;
they are antigenic and are the source of ABO blood group antigens. There are two different types of
glycosphingolipids: neutral and acidic. Neutral glycosphingolipids include: cerebrosides (simplest) made of
ceramide and a glucose/galactose molecule (glucocerebroside/galactocerebroside) and globosides (ceramide
oligosaccharides) which are a glucocerebroside with an additional monosaccharide. Acidic glycosphingolipids
are globosides with a NANA attached.
2. Describe the pathway of sphingolipid synthesis/catabolism and what disease conditions result from defects of
enzymes involved in these (in notebook) the enzymes involved are collectively called acid hydrolases
3. How is sphingosine synthesized? How and where is ceramide synthesized? Ceramide plays a key role in
maintaining the skin’s water-permeability barrier. Sphingosine synthesis: palmitoyl CoA + serine sphinganine
+ LCFA ceramide (contains sphingosine and FAs). This occurs in the ER then is packaged to the Golgi that
sends them to the PM where they are used until they need to be degraded in lysosomes.
4. What is the cellular function of lysosomes and what role do they play in the catabolism of sphingolipids? The
sites of lipid degradation are in lysosomes which is where the acid hydrolases are located that breakdown the
sphingolipids. If one of the enzymes is working properly then the lysosomes can be filled with accumulated
lipids which can cause megaly of the organelle and destroy other cells.
5. What is the genetic defect in Gaucher disease and what particular cell types are affected the most in this
disease? What substrate accumulates to significant levels in the disease? (in attached notes)
6. What are the common types of mutations that result in this disease and what are the patterns of inheritance?
What population is most commonly affected? (in attached notes)
7. Describe the histopathological feature of Gaucher disease and explain what accounts for this. Why does it
pose a problem for the liver and spleen? (in attached notes)
8. Differentiate between the features of Type I, Type II and Type III Gaucher disease. (in attached notes)
9. Explain the reasons for the patient’s pancytopenia, avascular necrosis of the femoral head and neurological
symptoms of this disease (why do they have their symptoms)? (in attached notes)
10. How can this disease be diagnosed by laboratory investigation? (in attached notes)
11. Describe the treatment options for this condition and the rationale for their uses and setbacks to their uses.
(in attached notes)

I-Cell Disease (Mucolipidosis Type II)
*Glycoproteins have a wide range of functions. What are glycoproteins, they are proteins with an
oligosaccharide attached to it. There are different types of glycoproteins: Mucins and Erythropoietin (EPO).
Mucins are heavily glycosylated protein produced and released by epithelial cells. They contain a high number
of threonine and serine residues, which means they can form many o-glycosylation linkages. The highly-
glycosylated characteristics of mucins makes them resistant to proteolysis and gives them the ability to absorb
water. Mucins form mucous barriers that lubricate and protect epithelial tissue. Although most mucins are
released into the extra cellular matrix. Some remain attached to the membranes.
1. What are the distinguishing clinical features of I-Cell disease? 2. How can you differentiate I-Cell disease
from Hurler disease? I-cell disease (mucolipidosis II) is a rare inherited metabolic disorder characterized by
coarse facial features, skeletal abnormalities and mental retardation. The symptoms of I-cell disease are similar
to but more severe than those of Hurler syndrome. The symptoms associated with this disorder typically become
obvious during infancy and may include multiple abnormalities of the skull and face and growth delays. I-cell
has an earlier onset of symptoms, gingival hypertrophy and corneal opacities are more severe in I-cell,
radiographic changes in older children with I-cell are nonspecific like in Hurler’s.
3. What explains the difference in the intracellular and extracellular activities of lysosomal enzymes in I-Cell
disease? Biochemically I-cell disease is characterized by excessive secretion of newly synthesized lysosomal
enzymes into bodily fluids and loss of intracellular activity in fibroblasts.
4. Differentiate I-Cell disease from Gaucher disease, also from Pseudo-Hurler disease. Increase lysosomal
levels in serum cannot distinguish between I-cell and pseudo-hurler. Phosphotransferase deficiency in I-cell is
total while in PHD it can have up to 10% efficiency. Enzyme levels: -mannosidase and -glucuronidase are
higher in PDH than in I-cell but both have high levels compared to controls; -fructosidase, -glycosaminidase,
and -glucosaminidase levels are higher in I-cell than PHD but both activities are higher than control. Gaucher
disease is associated with high glucocerebroside in lysosomes, but in I-cell the accumulation of substrates in the
cell is not as much as in Gaucher disease. Also, Gaucher disease does offer enzyme replacement as a possible
treatment option.
5. Describe the process of clathrin-mediated endocytosis and N-linked glycosylation. What are the roles of the
rough ER and Golgi in intracellular protein trafficking? RER Golgi binding to MPRs Acidified
department lysosome. N-linked glycosylation is the attachment of an oligosaccharide, a carbohydrate
consisting of several sugar molecules, sometimes also referred to as glycan, to a nitrogen atom, this occurs in
the Golgi. This occurs through phosphotransferase.
6. Describe how lysosomal enzymes are targeted to the lysosomes and identify the functions of
phosphotransferase, M6P, MPRs. RER Golgi binding to MPRs Acidified department lysosome. M6P is
phosphorylated by phosphotransferase. Once it is attached, the molecule can now attach to MPRs that transfers
the lysosomal enzyme to the acidified compartment. There are two distinct MPRs: a smaller one that is cation-
dependent and a larger one that is cation-independent
7. Describe the implicated molecular pathologies in I-cell disease and how that varies from ML III. In I-cell,
lysosomal enzymes are not modified by the addition of mannose 6-P because M6P is not phosphorylated by
phosphotransferase. Thus, they are not segregated by the MPRs into the appropriate vesicles in the TGN and
instead are carried to the cell surface and secreted (RER Cell Surface).Golgi
8. How can the defect in I-Cell disease account for the symptoms observed in the patient? The symptoms of I-
cell disease develop due to deficiencies of a variety of lysosomal enzymes in the cells of the body causing an
abnormal accumulation of certain fatty substances (mucolipids) and certain complex carbohydrates
(mucopolysaccharides) within the cells of many tissues of the body.
9. Describe the possible management options for I-Cell disease and the challenges to their success. Enzyme
replacement is only available for Gaucher disease, Fabry disease, and MPS 1. Enzyme correction in golgi is a
possible remedy for I-cell. Bone marrow transplant has improved biochemical and clinical symptoms of I-cell
probably because hematopoietic progenitors can donate lysosomal enzymes to the deficient cells in all tissues of
the host. Gene replacement is another idea as well as peptide targeting systems.

HMG Co-A Lyase Deficiency
1. What is metabolic acidosis? How is it clinically diagnosed and what are the possible causes? Metabolic acidosis is a
disorder that occurs when the body produces excessive amounts of acid, such as ketoacids or lactic acid; the kidneys are
unable to remove enough acid produced from normal metabolism. Individuals with HMG-COA lyase deficiency cannot
tolerate the increased mobilization of leucine from muscle proteins during fasting and will quickly decompensate and
develop metabolic acidosis because proper catabolism of leucine cannot occur, and HMG and its precursors are excreted.
2. What are examples of branched amino acids? Describe the pathway of branched-chain amino acid metabolism.
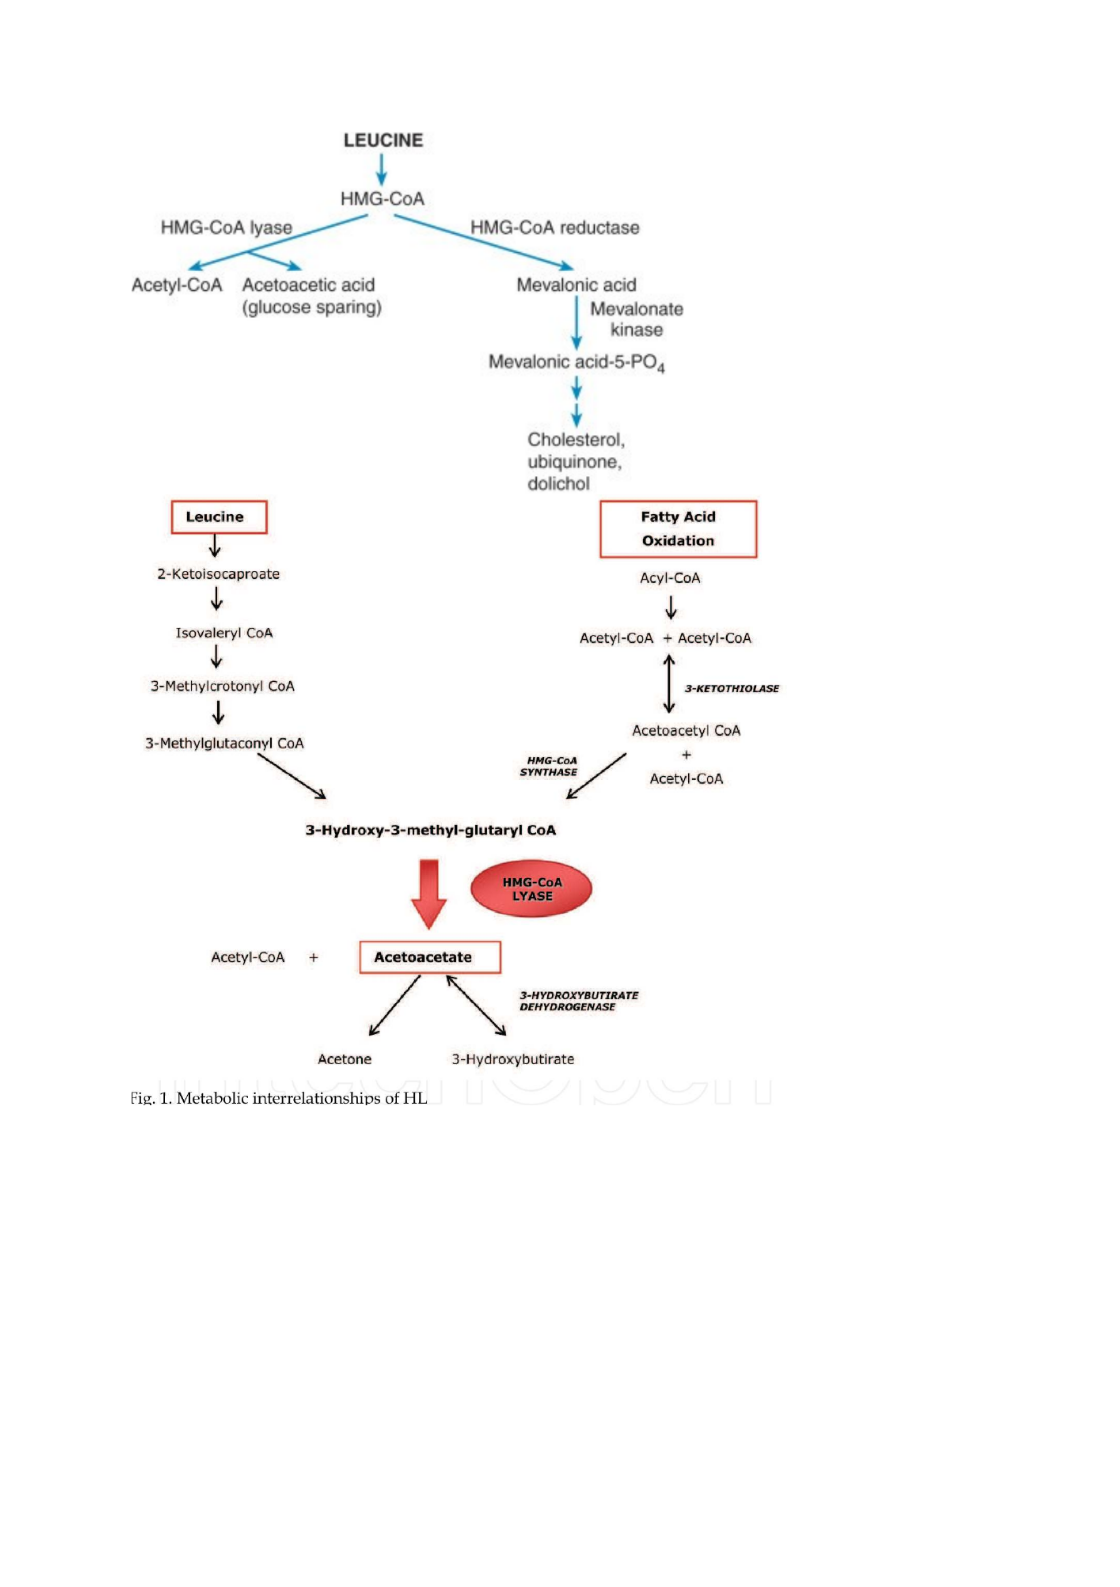
Branched amino acids are leucine, isoleucine, and valine are catabolized in the mitochondria. In leucine catabolism, the
amino group of the leucine is removed making -ketoisocaproate isovaleryl-coa 3-methylcrotonyl-coa 3-
methylglutaconyl-coa HMG-CoA acetoacetate and acetyl-coA
3. What are the causes of other types of organic acidurias? How is HMG-CoA lyase deficiency different in presentation
from the others? The other types of organic acidurias include methylmalonic aciduria, propionic aciduria, and isovaleric
aciduria, but the urinary organic acids create a unique profile for each disease. In HMG-CoA lyase deficiency the urine
organic acids include 3-methylglutaric and HMG acid. Also, in HMG-CoA lyase deficiency hypoglycemia is not
associated with increased ketone bodies because ketogenesis doesn’t make its full effect in this disease.
4. Are patients with HMG-CoA lyase deficiency always symptomatic? What are common precipitants of their symptoms?
Why did this patient have an aversion for oral feeding? No, not all patients are symptomatic because metabolic
decompensation often results after acute illness especially with fever, vomiting, diarrhea, and dehydration. Common
symptoms include metabolic acidosis, organic acidurias, hyperammonemia, hepatomegaly, and hypoglycemia. The patient
had an aversion for oral feeding because of her chronic gastric acidemia, reflux, frequent hospitalizations, hypotonia, and
developmental delay.
5. Explain the process of ketogenesis and why you think leucine is said to be a ketogenic amino acid. Ketogenesis is an
alternative pathway in which the A-CoA from -oxidation is used to create ketone bodies like -hydroxybutyrate and
acetoacetate which can be further oxidized by tissues that retain an active TCA cycle. Leucine is an amino acid that can be
degraded directly into acetyl-CoA, which is the precursor of ketone bodies
Leucine and lysine are the only solely ketogenic AA (the L-amino acids). FITTT symbolizes the five ketogenic and
glucogenic amino acids, Phenylalanine, Isoleucine, Threonine, Tryptophan, and Tyrosine
6. Explain what happens to serum carnitine levels in HMG-CoA lyase deficiency. Why is carnitine supplementation
critical in managing patients with HMG-CoA lyase deficiency? The serum carnitine levels decrease in HMG-CoA lyase
deficiency. Carnitine is essential for transporting LCFA across the mitochondrial membrane for -oxidation. Carnitine
also facilitates the removal of xenobiotics.
7. How is HMG-CoA lyase deficiency different from maple syrup urine disease? Maple syrup disease the deficient amino
acids are leucine, isoleucine, and valine.
8. What is the cause of the hyperammonemia, hypoglycemia, hepatomegaly and hypotonia in this patient? No -oxidation
means that there is an increase of lipids in hepatocytes which causes hepatomegaly, which means that there is no ATP
available from -oxidation which impairs urea synthesis and results in hyperammonemia. Since there is no ATP (and A-
COA for OAA syn) available for gluconeogenesis, glycogen storages are depleted causing fasting hypoglycemia.
9. What is the role of ATP in ureagenesis and gluconeogenesis? Why is frequent feeding important to managing patients
with HMG-CoA lyase deficiency? no ATP available from -oxidation which impairs urea synthesis and results in
hyperammonemia. Since there is no ATP (and A-COA for OAA syn) available for gluconeogenesis. Frequent feeding is
important because you don’t want the patient to undergo a fasting state which can lead to hypoglycemia.
10. Why does fatty acid oxidation become depressed in HMG-CoA lyase deficiency?
11. What is the significance of dietary restriction in the control of symptoms in this patient? To make sure that the patient
doesn’t go into a fasting state and also that there is enough leucine for growth.
LEUCINE
HMG-CoA
HMG-CoA
lyase
HMG-CoA
reductase
Acetyl-CoA
Acetoacetic
acid
Mevalonic
acid
(glucose
sparing)
Mevalonate
kinase
Mevalonic
acid-5-PO,
Cholesterol,
ubiquinone,
dolichol
Oxidation
2-Ketoisocaproate
Acyl-CoA
“ey
CoA
Acetyl-CoA
+
Acetyl-CoA
3-Methylcrotonyl
CoA
3-KETOTHIOLASE
v
Acetoacetyl
CoA
3-Methylglutacany!l
CoA
HMG-CoA
+
SaaS
Acetyl-CoA
3-Hydroxy-3-methyl-glutaryl
CoA
Acetyl-CoA
+
3-HYDROXYBUTIRATE
DEHYDROGENASE
Acetone
3-Hydroxybutirate
Fig.
1.
Metabolic
interrelationships
of
HL
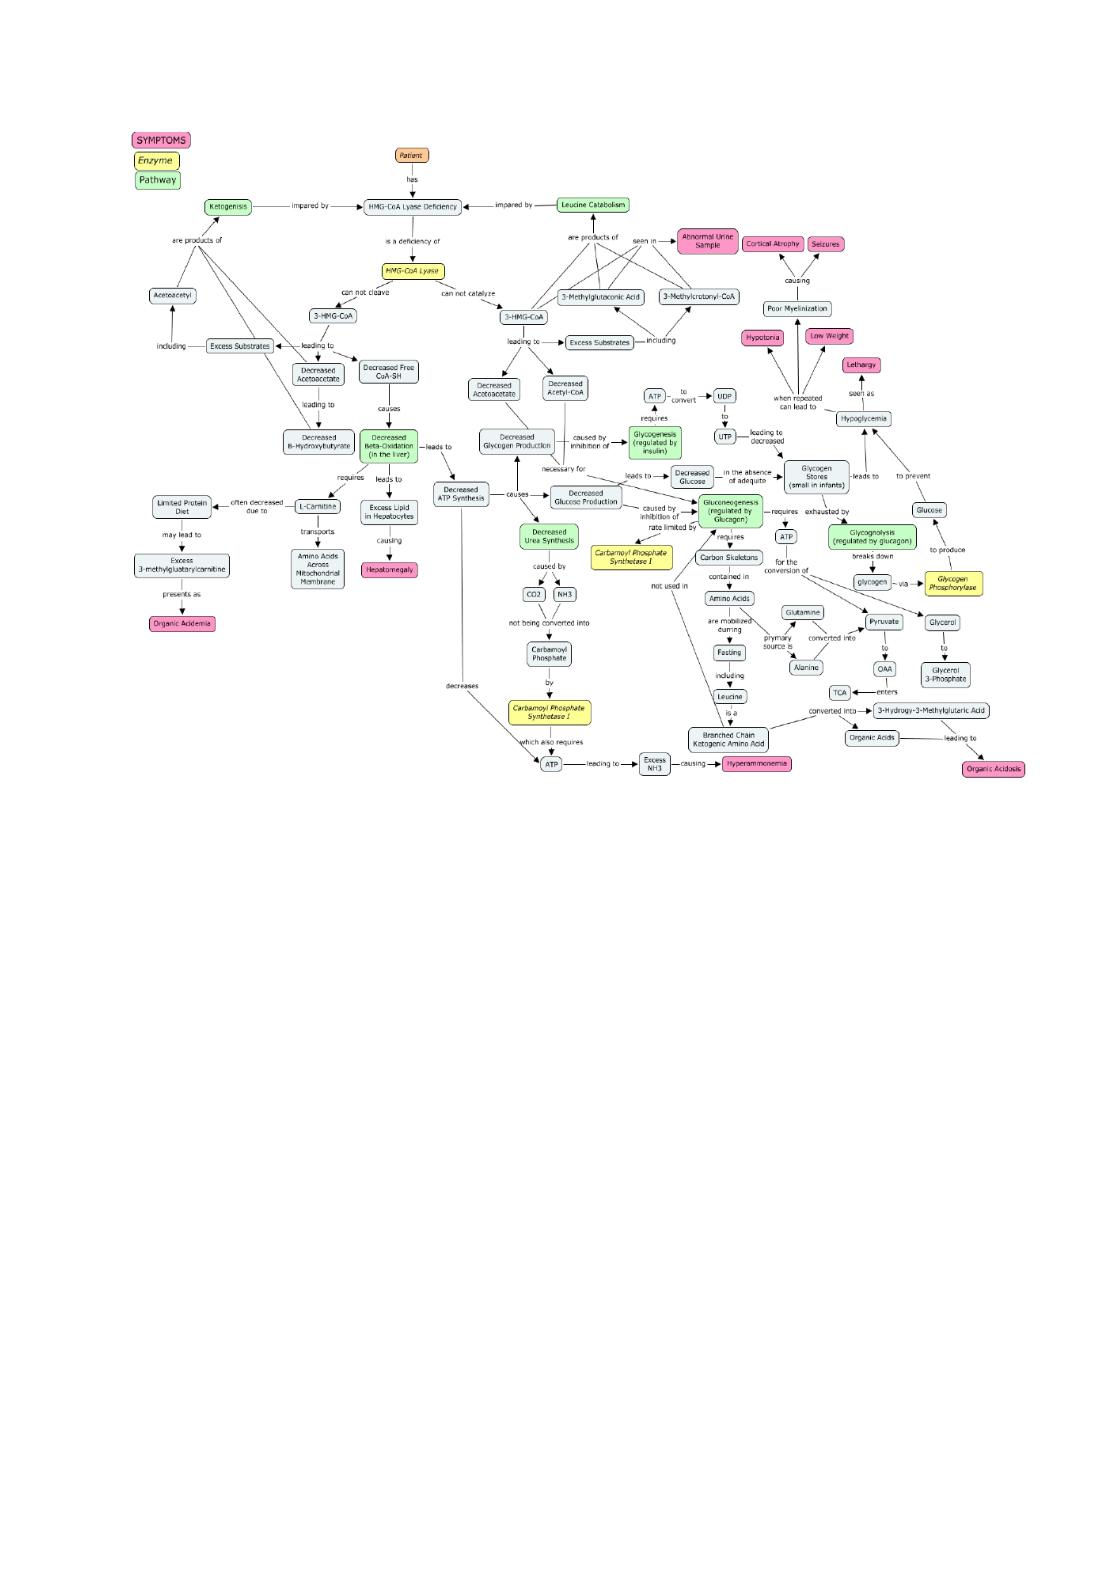
*remember that ketogenesis (liver) and gluconeogenesis (liver) occurs when one is in a fasting state.
Gluconeogenesis requires branched amino acids and ATP from B-oxidation of fatty acids in which the reducing
agents can flow directly to the ETC. The extra A-COAs from B-oxidation go through ketogenesis
Fasting State insulin glycolysis gluconeogenesis ketogenesis lipolysis -oxidation glucagon
cortisol catecholamines

