


Impact of Religion on Mental Health Care Use
Among African Immigrants in the United States
Chapter 1: Introduction to the Study
Mental health illnesses are the leading causes of disability worldwide (Anxiety
and Depression Association of America [ADAA], 2020). One in every five adults suffers
mental illness every year in the United States (National Alliance of Mental Illness
[NAMI], 2021). The World Health Organization (WHO, 2020) reported that worldwide
almost 75% of people with mental health problems remain untreated, contributing to
suicides, more disability, and overall poor quality of life. African immigrants in the
United States are the fastest-growing immigrant group, which has continued to double
every decade since 1970 (Omenka et al., 2020; Tamir, 2022; U.S. Census Bureau, 2020).
In 1980, there were 816,000 African immigrants in the United States compared to 4.2
million in 2016 (Tamir, 2022). Despite being more likely to have health insurance than
immigrants from other countries and being more highly educated than American-born
citizens, their mental health care use remains relatively low with reliance on family
support and religion rather than medical care (Adu-Boahene et al., 2017; Anderson, 2017;
Derr, 2016; Echeverria-Estrada & Batalova, 2019; Omenka et al., 2020).
Adu-Boahene et al. (2017) reported that underuse of mental health services is
significantly more prevalent among immigrants residing in the United States for periods
less than 10 years. African immigrants are more prone to mental disorders as they try to
assimilate and acculturate to the dominant culture, face discrimination, and experience

language barriers (Omenka et al., 2020). Immigrants from war-torn countries are at
greater risk for mental disorders as they seek asylum in their new countries while
severing all ties with their countries of origin (Adu-Boahene, 2017).
Mental health care is paramount to ensure health and wellness. The low levels of
mental health literacy and high levels of mistrust, apprehension, and stigma experienced
by African immigrants in the United States contributes to the underusage of formal
mental health care by this population (American Psychiatric Association [APA], 2017;
American Foundation for Suicide Prevention [AFSP], 2019; Mental Health America
[MHA], 2020; WHO, 2020). Religion, which includes traditional faith and values, serves
as the cornerstone of wellness among the Black population in the United States which
includes African immigrants (AFSP, 2019; Wharton et al., 2018). There is a higher
reliance on cultural avenues and spirituality for overall wellbeing as well among African
immigrants (Omenka et al., 2020; NAMI, 2020). Understanding the role of religion in
mental health care use is consequently paramount to better comprehend and collaborate
mental health care for African immigrants in the United States
In this chapter, I will cover the background of this study, present the problem
statement, describe the purpose of the study, state the research questions, describe how
the theoretical framework will be used, define the nature of the study, describe the
assumptions, scope, delimitations, and limitations, and finally present the significance of
the study.

Background
African immigration to the United States began in 1600 from forced immigration
due to slavery and has continued into voluntary immigration as world globalization
occurs (Tamir, 2022). There has been a 71% increase in the United States African
immigrant population since 2000, making one in every 10 Black persons living in the
United States foreign born. The top five African countries contributing to the migration
are Nigeria, Ethiopia, Egypt, Ghana, and Kenya, accounting for more than half of
foreign-born Africans in the United States (Anderson, 2017; U.S. Census Bureau, 2020).
West African immigrants make up about 44% of African immigrants to the United States
immigrants, with East African's making up 36% of this population with the remaining
countries contributing from the south and Northern Africa (U.S. Census Bureau, 2020).
Sackey-Ansah (2020) reported that the emigration of African immigrants to the
United States results from various push-pull factors. The push factors providing Africans
momentum to leave their native countries include political unrest, economic hardships,
inflation, or recession. In contrast, the pull factors encourage Africans to emigrate to the
United States, such as higher education, better opportunities, and dream actualization
(Sackey-Ansah, 2020). Most of the immigration from Africa is voluntary from
reunification to their relatives in the United States, attaining higher education, increased
globalization to higher-income countries, and diversity visa programs (Commodore-
Mensah et al., 2018; Echeverria-Estrada, & Batalova, 2019; Tamir, 2022).
Compared to other immigrant groups in the United States, African immigrants are
more likely to have higher education with bachelor's degrees or higher and be

Englishspeaking at home with a middle-class socioeconomic status (Tamir, 2022).
However, Tamir (2022) noted differences in education and income depending on country
of origin, with Nigerian and Kenyan immigrants being more likely to have a bachelor's or
master's degree and fall in middle to high-income categories while Somalians and
Ethiopians are less likely to be educated. Education levels of immigrants are also noted to
be dependent on the political stability of the country of origin, with refugees from
politically unstable countries being less likely to be educated and consequently having a
lower socioeconomic status (Tamir, 2022). African immigrants tend to settle in larger
metropolitan areas, with more than one third of all African immigrants to the United
States. residing in New York City, Washington, DC, Dallas, Minneapolis, or Atlanta
(Covington-Ward et al., 2018; Echeverria-Estrada & Batalova, 2019; Omenka et al.,
2020; Tamir, 2022).
Problem Statement
Previous and current literature shows that it is paramount to have more research
among African immigrants in the United States as it is the fastest-growing group of
immigrants in the United States (see Adekeye, 2014; Agbemenu, 2016; Ekwonye et al.,
2021; Freeland et al., 2020; Nantwi et al. 2017; Omenka et al., 2020; Shoup et al., 2021;
Venters et al., 2011). Still, few studies have been conducted to understand the specific
health needs of African immigrants. Mental illness is especially crucial as it is the highest
cause of disability among the 18-65 age group and has detrimental effects on the
economy with the loss of workforce and wages (WHO, 2020). Delayed seeking of mental
health services is also associated with increased chronicity and severity of mental illness,

which therefore results in use of emergency care rather than preventative and
maintenance measures, which are less costly and more effective (MHA, 2020).
Health needs among African immigrants remain under researched as few studies
are done among African immigrants, and studies done among Black people in the United
States do not differentiate between African immigrants, Caribbean immigrants, or
African Americans (MHA, 2020; Pew Research, 2022). There is thus a lack of knowledge
about African immigrants' health needs (Venters et al., 2011). Venters et al. (2011) noted
that despite mental illness being the top three diagnoses identified among African
immigrants, referral to mental health services remains unused or even suggested by health
care providers. As such, the issue with the underuse of mental illness care is multifocal.
Religion cannot be understated in its role among African immigrants and their
wellness. Multiple authors have noted that religion has a role in healthcare use, but the
specific role is not clearly described (see Adekeye, 2014; Agbemenu, 2016; Ekwonye et
al., 2021; Freeland et al., 2020; Nantwi et al., 2017; Shoup et al., 2020). Understanding
how religion impacts decisions about mental health care use can help identify and attempt
to meet the needs of the fastest-growing immigrant group in the United States.
Purpose of the Study
In this study, I built on available literature and provide a qualitative exploration of
how religion impacts mental health care use among African immigrants in the United
States. In understanding the social problem from the immigrant’s perspective,
information can further inform clinical care through cultural competence to reduce
disparities that immigrants face and thus improve quality of life. The purpose of this

qualitative study was to understand the experiences of African immigrants in the United
States with the mental health system and how religion influences mental health care use
among this population.
Research Questions
RQ1: What are the experiences of African immigrants in the United States with
mental health care use?
RQ2: How does religion influence mental health care use among African immigrants
in the United States?
Theoretical Framework
Ajzen (1985) developed the theory of planned behavior (TPB) to describe and
predict behaviors. The theory is a refinement of the theory of reasoned action by Ajzen
and Fishbein (Boslaugh, 2019). In TPB it is assumed that behaviors are under a person’s
will, and hence the theorists seek to understand the relationship between human behavior
and motivation (Boslaugh, 2019). The TPB indicates that attitude towards behavior,
perceived behavioral control, and subjective norms are the main themes that influence
behavior patterns (Asare, 2015; Tornikoski & Maalaoui, 2019; Vaismoradi et al., 2016).
Using the themes of TPB allows a researcher to conduct thematic analysis for both latent
and manifest content, with coding being completed through probable subthemes.
Behavioral intention is the motivational factor influencing behavior; the more robust the
intention, the more likely the behavior’s engagement (Asare, 2015).
The attitudes towards behavior are the favorable or unfavorable appraisal from the
behavior. Attitudes are comprised of behavioral beliefs and outcome evaluations (Asare,

2015). If the appraisal is unfavorable, then engagement would be unlikely in the behavior.
Understanding the behavioral beliefs of African immigrants in the church and the
appraisal results towards health-seeking behaviors may increase cultural competence,
which increases collaboration between religion and the medical providers (Asare, 2015).
The subjective norm is the social pressure to perform or not to perform a specific
behavior. This construct is vital in immigrant societies due to the value of community
support and religion for total wellbeing, which can influence seeking or not seeking
formal mental health care (Asare, 2015; Agbemenu, 2016). Behavioral control is the ease
or difficulty of performing behavior that can be used in religious settings by removing
barriers such as stigma that increase the difficulty of medical seeking behaviors (Asare,
2015; Nantwi et al., 2017; Omenka et al., 2020; Vaismoradi et al., 2016)
Nature of the Study
To address the research questions, I employed an ethnographic qualitative design
using semistructured interviews and field notes for data collection. This design yielded
descriptive qualitative data to further improve an understanding of the role of religion in
mental health care use among African immigrants in the United States. Qualitative
research is an iterative process that allows a deeper understanding of a community
through proximity (Aspers & Corte, 2019). Ethnographic studies offer a comprehensive
understanding of cultural groups within a people group allowing the reader to understand
the culture group characteristics such as religion among African immigrants (Morgan-
Trimmer &Wood, 2016).

Semistructured interviews allowed for the integration of both structured
questionings on interviews and allow the researcher to probe deeper in pursuit of detailed
responses. The flexibility is thus an added merit to the study design as new ideas can be
obtained that were not previously thought of (DeJonckheere & Vaughn, 2019). Individual
interviews may also allow the divulging of information from participants without
worrying about stigma or how others would perceive them, which is an essential and
crucial element as the underutilization of mental health care among African immigrants
has been partially attributed to cultural stigma issues (MHA, 2020; Omenka et al., 2020).
The fundamental concepts of and the phenomenon of the investigation was religion
among African immigrants in the United States.
I collected the data from African immigrants of using semistructured interviews.
The study was limited to the greater Houston metropolitan area. Nonprobability
purposeful and snowball sampling strategies were used with recruitment taking place in
places of worship and restaurants that serve African immigrant communities in the
Houston area. Ten interviews were conducted, and data saturation was reached.
Interviews took place in the conference room of a local library as well as through Zoom.
Field notes and audio record were taken on each of the interviews. Zoom was used for
transcription while Dedoose software was used for coding and assistance with analysis.
All data was stored in my personal computer, which was password protected to ensure no
unauthorized persons could have access. Analytic induction and thematic analysis were
used for data analysis to identify emerging themes related to the experiences of African

immigrants with the mental health system and the ways in which religion affects mental
health use among the African immigrants sampled (see Braun & Clarke, 2014).
Definitions
African immigrants: People born on the African continent who have immigrated
into the United States for permanent residence (Tamir, 2022).
African traditional religions: Systems of faith in worship of ancestors, mountains,
higher powers such as witchcraft, sorcery, and the dead (Nantwi et al., 2017; Omenka et
al., 2021).
Coping: Enduring and adjusting with unpleasant outcomes, such as mental
diseases, to defeat and deal with the events (Omenka et al., 2021; WHO, 2020).
Disability: A condition that causes impairment to the recipient making it difficult
to work or interact with normalcy with the rest of the population (Centers for Disease
Control and Prevention, 2021).
Formal mental health care: The use of a health provider for the services of mental
health illness and following through with instructions or treatment provided (Wharton et
al., 2018).
Health providers: Members of the health system that provide care to patients such
as nurses, nurse practitioners, doctors, therapists, and psychiatrists.
Informal mental health care: The use of friends, family, or religion to help cope
with mental illness.

Mental health care use: The use of formal health care systems and resources for
health such as hospitals, clinics, psychiatric rehabilitation, psychiatrists, therapists,
psychologist, doctors, or nurses for mental health issues (Omenka et al., 2021).
Mental health literacy: The knowledge and understanding of mental disorders that
aid in easy recognition of the disorders to foster treatment and prevention.
Mental illnesses: Collective term of diseases affecting mental and cognitive health
such as depression, anxiety, psychosis, dementia, and schizophrenia (MHA, 2020).
Religion: Systems of faith and belief in the worship of a higher being such as God
(Wharton et al., 2018).
Religious leaders: Leaders of various religious entities such as priests, clergy,
traditional leaders, elders, and Imams.
Assumptions
Assumptions in the study are aspects I assumed to be true. I assumed that
participants would be forthright in sharing their experiences and would engage with me to
answer the questions in an in-depth manner. Their honest and truthful opinion was also
expected. Another assumption was that African immigrants would have similar
experiences in the immigration process. Their experiences of immigration and relocation
were also assumed to be relatively similar in this study. The assumptions were necessary
for the study because I desired to gain a deeper understanding of the participant's
experiences of the role of religion in their lives and cultures in influencing mental health
care use, to make correct inferences.

Scope and Delimitations
The scope of the study was limited to African immigrants who were currently
living in the United States. The range of delimitations were African immigrant residents
in the United States, with a religious preference. The study was limited to adults 18 years
and older. The study excluded those below 18 years. All participation was voluntary, and
all participants were provided with informed consent. The study investigated African
immigrants’ experiences as it related to mental health care use in the United States but
did not include direct observation. Instead, I relied on participants descriptions of their
experiences in their own words.
Limitations
The study sample was small so generalization to all African immigrants in the
United States was not assumed. The fear and stigma associated with mental illness among
African immigrants could also have generated false information to me from fear of
disclosing personal or family experiences with mental illness. The design use of
semistructured interviews may have also been a limitation with participants who did not
feel comfortable divulging more in-depth information to me. Biases associated with
purposive sampling such as selection bias may have been possible as all participants of
the study had the defined characteristics to fit the study. Consequently, there was a lack
of random sampling that avoided similar possible characteristics in demographics,
religious experiences, family dynamics and history of their backgrounds.
To address these the limitations, I used semistructured interviews to probe for
further information from the participants if the information provided was unclear or too

generalized; thus, the provision of detailed information was likely more accurate. Use of
purposeful silence was used to allow the participants to divulge more information (see
Bengtsson & Fynbo, 2018). To enhance comfort in disclosing information, interviews
were more informal with some general questions before easing into the actual questions.
Questions were also conversational rather than standardized to avoid the perception of a
formal interview and to ease anxiety (see Aspers & Corte, 2019). This required me to
familiarize myself with the questions and avoid excessive writing during the interview to
pay attention to the interviewee. The biases in purposive sampling were combated by a
clearly defined target population and sampling frame from which the group of
participants was drawn (see Andrade, 2021)
Significance
Information gained from this study may be used to equip religious leaders and
health care providers with the knowledge needed to foster mental healthcare use among
African immigrants to the United States. Increasing mental health care use fosters
improved mental health outcomes and wellness thus contributing to positive social
change among African immigrants in the United States (MHA,2020). Gained knowledge
from the study increases available data on African immigrants in the United States, which
can foster an increase in cultural competency among providers dealing with an
everdiverse population. The information gained from the study may also be used to
integrate cultural competence in clinical practice regarding African immigrants in the
United States which then adds to the scant data available for providers on African
immigrants which would advance available knowledge for referencing.

The information gained may be used to develop cultural competence trainings for
mental health providers working with African immigrants therefore improving mental
health wellness among African immigrants in the United States. The study information
may also be used to increase collaboration between religious institutions and healthcare
providers to provide holistic care to African immigrants. This study is also significant in
that the information deducted may be used to inform positive social change by guiding
policymakers and clinicians in not only cultural competence in the treatment of African
immigrants but also the importance of including religiosity in the treatment plans which
is beneficial for African immigrant mental health and wellness.
Summary
African immigrants are the fastest-growing immigrant group in United States.
Black Americans continue to use mental health care at lower rates compared to other
races with high reliance on religion though how religion impacts their mental health
wellness remains unclear (Omenka et al., 2020). Mental illness is the highest contributor
of disabilities among middle-aged adults worldwide with economic, productivity, and
quality of life ramifications (MHA, 2020; WHO, 2020). Despite studies conducted with
other immigrant groups in relation to mental health care use, there is scant data on
African immigrants’ mental health. This study may provide a greater understanding of
how religion influences mental health care use among African immigrants. The
information gained from this study will not only contribute to literature available on
African immigrants’ mental health but also provide collaborative ways in which both
religious institutions and health providers can use the knowledge to provide holistic

mental health care to African immigrants to improve their mental health outcomes.
Chapter 2 will provide a review of the relevant recent literature on this topic, discuss the
relevance of the TPB to the study as well as describing how the theory was used in the
study.
Chapter 2: Literature Review
Mental illness remains the leading cause of disability worldwide, with one in
every five adults having suffered a mental illness in the United States (ADAA, 2020;
NAMI, 2021; WHO, 2020). Mental health care use remains low, with WHO (2020)
reporting that 75% of people who have mental illness remain undiagnosed and untreated.
African immigrants in the United States have lower mental health care use despite having
health insurance and having higher education which indicates the need to understand the
experiences that affect health care use (Omenka et al., 2020; Shoupe et al., 2020).
Religion among African immigrants is fundamental, with Ajima and Ubana
(2018) attributing the health and wholeness of Africans to their religious beliefs and
practices. Despite data showing the social problem of underuse of mental health services
among African immigrants in the United States and studies indicating that religion plays a
role, the ways and extent of religion's role in mental health care underutilization is not
fully understood. In addition, most data is from studies of West African immigrants to the
United States, with scant data on immigrants from other African countries. As such I
examined the role of religion among African immigrants in the United States by
recruiting a wide variation of African immigrants for the study. This chapter will include
a description of the literature search strategy, the study's theoretical foundation, a review

of the literature related to critical variables and concepts of the study, and a
summary/conclusion.
Literature Search Strategies
Peer-reviewed journals, scholarly articles, and nationally recognized sources were
used in an iterative process to gather information for the literature review. The keywords
used in the searches were African immigrants in the United States, mental health/mental
disorders/psychiatric illness, mental health care use, and religion/spirituality/faith used
interchangeably in databases to provide results. Combined search terms included African
immigrants in the United States and mental health; African immigrants in the United
States and religion; role of religion among immigrants in the United States; Blacks,
religion, and mental health; spirituality among African immigrants and health-seeking
behaviors; stigma among African immigrants on mental health; and the role of the
church and mental health among Blacks. The databases used were MEDLINE, CINHAL,
PsychINFO, PubMed, Science Direct, EBSCO, ProQuest dissertations, and Google
Scholar. A combination of search terms was used to provide relevant journals. Results
were limited to peer-reviewed journal articles published between 2016 and 2021.
Literature Review Related to Critical Variables and Concepts
Religion is essential in the larger Black community in the United States, including
African Americans, African immigrants, Caribbean immigrants, et cetera, with more than
90% attributing wholeness and wellness to religious aspects (MHA, 2020; Tamir 2022).
The role of region among African immigrants cannot be underestimated. A review of the

literature related to critical variables and concepts of the study which included a deeper
understanding of religion, Mental illness and acculturation was hence discussed.
Religion
Sackey-Ansah (2020) and Omenka et al. (2020) viewed religion as any belief in
higher power through organized institutions such as Catholicism, Christianity, Islam, or
traditional indigenous belief systems among African immigrants. In multiple studies
among blacks in the United States in which African immigrants are included, wholeness
and wellness are attributed to religion and right standing with God, thus affecting all
facets of life (Ekwonye et al., 2021; MHA, 2020; Nantwi et al., 2017; Omenka et al.,
2020; Saasa, 2019; Ting & Panchanadeswaran, 2016; Wharton et al., 2018). Various
facets of religion such as focus of life, coping, social support, wellness, and role of
religious leaders are discussed.
Religious Participation as the Focus of Life
Spirituality and religion have been used synonymously by Ting and
Panchanadeswaran (2016) as playing a role in an individual defining their meaning of
life. In a qualitative phenomenological study using semistructured interviews of 15
African Immigrant women from five different African countries who are now residing in
the United States, findings note that when faced with stressful situations, African
immigrant women choose the lens of religion to understand their circumstances and make
decisions pertaining their families in cases of domestic partner violence (Ting &
Panchanadeswaran, 2016). The study sought to understand African immigrant women’s
perceptions of faith-based leaders in Islam and Christianity after partner violence. The

results indicated feelings of being blamed, stigmatized, misunderstood, and lack of actual
practical help, such as women’s shelters were noted (Ting & Panchanadeswaran, 2016).
The study findings demonstrated that although religious institutions were the first line of
help among African immigrants in stressful situations, its role is not clearly defined as
beneficial for the women as results concluded hesitancy in seeking care due to the
findings of blame, stigmatization, and being misunderstood (Ting & Panchanadeswaran
(2016).
Like the findings of Ting and Panchanadeswaran (2016), Nantwi et al. (2017), in
a qualitative exploratory research study of African immigrant college student’s perceived
identities (N=13), found that religion broadly frames their identity as African immigrants
in the United States by affecting their decision making. This was noted by constantly
referencing religion as their influencer in making decisions. Religion also influences how
they interact in their colleges by seeking like-minded individuals with similar beliefs and
health behaviors such as smoking or drinking (Nantwi et al., 2017). Religion thus plays a
role in their health-seeking behavior and use of health care services behaviors though the
extent of the role is not fully portrayed. Sackey-Ansah (2020), in a scoping review of
primary studies done on African immigrants, finds that religion is deeply ingrained
among African immigrants in decision making and view of life and thus that it is
inseparable from who they are which are similar findings as those of Nantwi et al.,
(2017). The study findings reported that the profoundly ingrained spiritual roots frame
African immigrants’ perceptions of health and health-seeking behavior, which
consequently alludes to studying how religion frames the mental health care use among

African immigrants in the United States (Sackey-Ansah, 2020).
Religion and Social Support
Religion among African immigrants does not only refer to spiritual practices such
as prayer or attendance to a religious institution but also the social aspect of providing a
support system and opportunities of social belonging among African immigrants
(Ekwonye et al., 2021; Omenka et al., 2020). Omenka et al. (2020), in a scoping review
of data of African immigrants in the United States from 1980 to 2016, using an open
coding approach, found that religion was not only viewed as relevance to God but also a
sense of belonging to the community. Immigrants not affiliated with churches or mosques
thus reported feeling alone and isolated (Omenka et al., 2020). Omenka et al. also found
that more than 90% of the scholarly journals reviewed noted religion as a source of
physical/spiritual wholeness and source of support. Support and social belonging are
essential in mental wellness since lack of support are attributed to poorer health outcomes
(MHA, 2020). As such, religious support among African immigrants is essential in
improving health outcomes.
Similarly, in an exploratory qualitative study examining the meaning of life and
the impact of COVID-19 on African immigrants in the United States, Ekwonye et al.
(2021) found that most participants reported that their informal relationships were mainly
formed in religious settings. The reduced face to face interactions led to feelings of social
isolation, anxiety, and lack of social satisfaction during the COVID -19 closing of public
gatherings (Ekwonye et al., 2021). The social isolation from lack of religious gatherings

and in-person meetings with friends and relatives contributed to overall feelings of
situational depression and anxiety among the study participants (Ekwonye et al., 2021).
Social support is thus essential among African immigrants as it provides a means of
belonging and coping in their new environments.
Religion and Coping
Religion aids in coping with various hardships such as discrimination among
African immigrants in the United States (Ekwonye et al., 2021; Nantwi et al., 2017;
Nguyen, 2020; Omenka et al., 2020). Religious affiliation is strongly associated with
coping (Saasa, 2019). In a largescale cross-sectional survey involving 409 African
immigrants in 42 out of 50 states, religion was found to serve as a buffer to
discrimination despite not offering moderation effects (Saasa, 2019). Passive religious
coping was found to exacerbate adverse effects and led to more isolation, deprivation,
underemployment, despite the higher levels of human capita among African immigrants
(Saasa, 2019). Among the participants use of active coping, defined in this study as the
use of formal health care, counseling, integration with American communities, and
moderation, was noted to reduce the effects of discrimination among the African
immigrants.
The same phenomenon is noted by the findings of Agyekum and Newbold (2016)
through an exploratory study of religious leaders, health practitioners, local group leaders,
and immigration counselors. Findings were that places of worship are essential to social,
spiritual, mental, physical, emotional wellbeing with reported increased perception of the
quality of life and belief of better health outcomes. The process or channels in which

religion improves the health outcomes or sense of belonging of African immigrants is,
however, not explored nor explained in the study (Agyekum & Newbold, 2016).
Agyekum and Newbold's study findings also note that when religion is actively practiced
with practical help such as employment, housing health, and support network, it was
found more helpful to the community. Active participation is, however, not defined or
qualified to different individuals and how it affects their health outcomes; hence deeper
understanding of the role of religious places of worship and mental health outcomes is
needed. Ting and Panchanadeswaran's (2016), like Agyekum and Newbold's, noted that
the presence of adverse outcomes did not deter the continued use of religion as the
primary influence on decision making among African immigrants. Religion thus
remained the primary influence in decision making among African immigrants. In
African traditions, seeking help and support from elders would be the first expected
appropriate behavior before turning to health professionals (Ekwonye et al., 2021).
However, with African immigrants in the United States, the scarcity of immigrant elders
in the community leads to reliance on spiritual leaders for support and coping when
facing difficult situations (Ekwonye et al., 2021; Nantwi et al., 2017). The phenomenon is
not only noted among younger immigrants but also older immigrants (Adekeye et al.,
2014). Adekeye et al. (2014), in a photovoice study done on a convenience sample in a
church involving young adults aged 13-18 years and elderly adults above 65 years old,
examined views of African immigrants on health resources access and found that most
participants, both the youth and the elderly, stated that religion and mental health went
hand in hand. They reported solutions to their problems and reported coping better in

faith-based organizations. The association of religion and perceived wellness in their
mental health is thus synergistic in the study (Adekeye et al., 2014). Similarly, Ojikutu et
al. (2018), in a qualitative study using a constructivist grounded theory to explore the
psychosocial mental health of 45 African immigrant women living with HIV, found that
most women reported ongoing persistent depressive symptoms, yet most were without
formal diagnosis or treatment. Of note, the women were all seeking treatment for HIV
and taking their medications but reported seeking religious faith leaders and friends to
cope with their emotional health rather than formal mental health care services (Ojikutu
et al., 2018). The reliance on religion for coping and survival of mental health issues was
thus more faith-based than formal healthcare-based despite access to health professionals
(Ojikutu et al., 2018; Adekeye et al., 2014). In qualitative studies such as Ting
and Panchanadeswaran (2016) and quantitative studies (Omenka et al., 2020), the
common themes of religious coping for physical and mental issues were clear. However,
how religion aids in coping was not elaborated. Ting and Panchanadeswaran (2016)
reported that African immigrant women domestic abuse survivors use religion to cope
with abuse through acceptance rather than seeking formal mental health care services.
However, the women also reported feeling marginalized, not getting help, and feeling
misunderstood by faith-based leaders suggesting religion may have negative impacts on
coping. Religion was consequently the frame and backbone of coping despite the social
issues faced among African immigrants.
The Role of Religious Leaders in Informal Caregiving
Wharton et al. (2018) used focus groups to investigate mental health use among

African American adults, which did not distinguish African immigrants and United
States-born African Americans, as noted in other studies (e.g., Agbemenu, 2016;
Freeland et al., 2020; Nantwi et al., 2017; Omenka et al., 2020) and found that informal
health seeking was most often to elders in the community and church clergy superseded
formal mental health care. Faith-based help was also more suitable for concrete life
events such as a death in the family rather than subjective events such as marital conflict
or abuse. The subjectivity of which events get help can lead to isolation among
immigrants undergoing the later events from fear of getting stigmatized hence they are
more unlikely to get assistance in such situations (Freeland et al., 2020; Ting &
Panchanadeswaran, 2016). Jangu et al. (2021) concurred in a qualitative study among
Black faith leaders from Christian and Islam religions using semistructured interviews in
a grounded theory. Authors found that 75% of faith leaders in the study felt a need to
address controversial subjects such as divorce, homosexuality, or issues such as HIV in
their congregations but feared detrimental effects such as reduced attendance, reduced
tithing, and alienating parishioners thus kept quiet about such subjects (Jangu et al.,
2021).
Despite the reliance of African immigrants on religion for direction, social
support, and coping, it is, however, not always provided by both leaders and some
religious organizations, as noted by the findings of Ting and Panchanadeswaran (2016).
Feelings of increased isolation, fear of being blamed, misunderstood, negative feelings,
lack of practical help, and stigmatization did not change the help-seeking behaviors

among African immigrants with noted continued reliance on elders and religious leaders
(Agyekum & Newbold, 2016; Nantwi et al., 2017; Ting & Panchanadeswaran, 2016).
Interestingly, a classic grounded theory study of 35 clergy faith leaders from the United
States, Africa, and India explored how religious leaders handle depression, suicidal
thoughts, posttraumatic stress disorder, and anxiety. Findings indicated that most clergy
members felt ill-equipped to handle mental illness despite the high influx of members
seeking mental healing, and they felt the need for higher training (Payne & Hays, 2016).
One sermon a year on topics of mental illness was the average among the faith leaders'
teachings to their congregations (Payne & Hays, 2016). The 35 clergy members noted the
reason for mental illness as varied, but none noted biological reasons or chemical
imbalances. They also all noted that faith leaders have a role in treating the mental illness
even though it would be collaborating care (Payne & Hays, 2016). Understanding how
religion plays a role in mental health care use is thus crucial as it continues to be the first
line for African immigrants, and the information gathered would contribute to the
knowledge gap of faith-based leaders on how to collaborate with mental health providers
in caring for their congregation.
Religion and Wellness
Religion is also attributed to overall wellness (Ekwonye et al., 2021). Ekwonye et
al. (2021) used an exploratory approach using phenomenology to explore African
immigrants’ meanings of life, and the findings note that religion was used as a lens for
viewing their lives and wellness. Their levels of wellness were attributed to the extent of
their alignment with their spiritual beliefs implying that the greater their religious

alignment, the more likely their perceived wellness and wholeness. It is essential to note
the findings from Ekwonye et al. (2021) did not attribute wholeness and wellness to
wealth, education level, socioeconomic status but to feelings of peace, contentment, and
quality of life despite their current health circumstances; thus, even those suffering from
health issues reported their wellness as good due to their religious alignment. Study
findings also note that about 75% of the African immigrants attribute their lives as
predestined by a higher power (Ekwonye et al., 2020). The attribution of wellness to
religion hence was noted as a contradiction to their health status as their connectedness to
religion was more of value than their actual health status (Ekwonye et al., 2020). The
author thus concluded that despite the role of religion being a lens of their circumstances,
the actual role remained misunderstood with its positive or negative implications towards
mental health care use as wellness was attributed to the connectedness to religion rather
than health status (Ekwonye et al., 2021).
Wellbeing is also studied by Areba et al. (2018) related to Somali immigrants in
Minnesota, where more than 2,200 Somalis reside. Somalians in the United States are
mainly refugees seeking asylum from political instability in their home country. Thus,
they have undergone traumatic experiences and may have long-term emotional
difficulties such as anxiety and depression (Areba et al., 2018). In a cross-sectional study
of 156 Somalis in Minnesota to examine associations of religious coping, signs of
depression/anxiety, and physical/emotional wellness, a high association of positive
religious coping such as acceptance of situations or using religion to forgive was
associated with a greater sense of wellbeing (Areba et al., 2018). Consequently, negative

religious coping such as displeasure with the clergy, questioning God's power was
associated with a lesser satisfaction with life, decreased overall wellness (Areba et al.,
2018). Areba et al.'s (2018) research thus mirrors Ekwonye et al. (2021) in noting that
religious affiliation was associated with a higher level of perceived wellness among
African immigrants irrespective of their current situations.
Mental illness
Mental illness among African immigrants is understudied as it is not considered
an actual disease in many African communities (see Agbemenu, 2016; Habecker, 2017;
MHA, 2020; Omenka et al., 2020; Shoup et al., 2021; Wharton et al., 2018;). Several
authors described mental illness as a "silent crisis" which remained underdiagnosed and
undertreated (see Ojikutu et al., 2018; Monnapola-Mazabane et al., 2021). Among
African communities, illness has often been described as a result of human inadequacies
(Agbemenu, 2016), a result of a curse on a family (Habecker, 2017), spiritual disharmony
(Senrich & Olusesi, 2016), from magical spells and voodoo (Ludwig & Reed, 2016),
from evil spirits and demonic interference (Omenka et al., 2020) and also from God’s will
(Agbemenu, 2016; Omenka et al., 2020; Senrich & Olusesi, 2016) thus the opposing
perspectives and attitudes towards mental illness among African immigrants enhance the
difficulty in the use of mental health care.
A higher risk of mental illness, especially depression, among immigrants due to
elements of immigration such as acculturation, premigration trauma, challenges in

obtaining citizenship, economic hardships, and expectations from their home countries
has been noted in both qualitative and quantitative studies (see Agbemenu, 2016,
Blackmore et al., 2020; Panettiere et al., 2017; Ojikutu et al., 2018;). Blackmore et al.
(2020), in a comprehensive scoping review of 21,842 journals from 2003 and 2020 using
a descriptive approach across 15 countries which included two African countries, found
high and persistent levels of post-traumatic stress disorder, depression, and anxiety
among immigrants in their host countries necessitating the need for continued mental
health care in their host countries. Panettiere et al. (2021) also noted a high incidence of
mental illness among African immigrants in the United States in a cross-sectional survey
conducted to measure anxiety and depression symptoms at the time of the study
(N=2,468) using the PHQ-4 assessment for depression. The authors noted that reasons for
immigration also impacted participants’ mental health, with traumatic immigration
resulting in higher incidences of mental illness. Immigration status, support in the host
country, employment status, and support system correlate to mental health status
(Panettiere et al., 2017). Immigrants depending on their immigration status were thus
noted to have increased stressors that could lead to mental illnesses.
Mental Health Care use among African Immigrants
MHA (2021) reports that 27 million adults with diagnosed mental illness remain
untreated. The Southern States, where a higher black population is highly associated with
less use of mental health care services (MHA, 2021). Despite reports of an increase in the
black population from immigrants from other countries, MHA (2021) data was not
categorized per immigrant group, but an overall reduced use of mental health care was

noted among black America. This section will cover the different aspects that affect
mental health care use among African immigrants
Mental Health Care Use in Africa. The status of mentally ill persons in
countries of origin affected mental health care use in the host country (Ojikutu et al.,
2021). Ojikutu et al.'s (2021) findings reported that many of the known and diagnosed
cases of mental illness were institutionalized in Africa, thus creating a phenomenon that
mentally ill persons could not live in the community with other people, leading to the fear
of a diagnosis of mental illness. Monnapola-Mazabane et al. (2021), in a scoping review
of peer-reviewed journals from 2008 to 2019, noted that mental illness in African
countries is not as professionally researched as other diseases like AIDS or Malaria, and
there is a lower density of mental health workers with a lower rate of mental healthcare
usage in African countries. Like the findings of Ojikutu et al. (2021), mentally ill persons
were also more likely to be institutionalized or hidden indoors by families for fear of
being labeled as crazy or being shunned from their communities (see
MonnapolaMazabane et al., 2021). The fear hence gives mental illness a negative
connotation as African immigrants leave their country. Ojikutu et al. (2018), in semi-
structured interviews of 45 African immigrants in the United States, finds that more than
half of the participants report the institutionalization of mentally ill persons in Africa
contributes to the overall view of mental illness as a negative disease that brings shame to
a person or family. Given the enculturation that occurs with African immigrants (see
Nguyen, 2020; Omenka et al., 2020; Shoup et al., 2020), the shame, stigma, and negative

stereotypes are carried forward to their new countries, thus the reduced rates of mental
health use in the United States despite the availability of services.
Conflicts with Religious Preferences. Controversies are also noted among faith
leaders’ teachings and access to care. An in-depth qualitative research study involving 17
African immigrants in the United States to explore the potential impact of culture, health,
and religious activities on health-seeking preventative behaviors, Freeland et al. (2020)
note that religious preferences delay access to care. Findings from the study were that
religious preferences affected health care use and especially attitudes towards prevention,
where 50% of the participants voiced that accessing preventative measures would
inadvertently cause them to have the disease by speaking it in their lives (see Freeland et
al., 2020). Religious preferences also supersede formal access to care despite the gravity
of the symptoms suffered (Freeland et al., 2020). The study is consistent with reports
from MHA (2020), which noted that there was delayed seeking of formal care for mental
illness among blacks in the United States due to seeking family, clergy, and other sources
hence leading to increased severity and chronicity of mental illness, among other
diseases.
Both Islam and Christian religions ascribe health and wholeness to God. Olukotun
et al. (2019) reported that findings from interviews conducted among African immigrants
reported that there were feelings among 75 % of the participants that reliance on western
medicine and doctors without seeking religious beliefs would be a conflict with their
beliefs and may bring ‘bad luck. Such notions can also delay seeking care among African
immigrants despite the awareness of mental illness in the family. Ekwonye et al. (2021)

and Ting and Panchanadeswaran (2016) reported the conflicts of religious and traditional
beliefs as barriers to health care use as help-seeking actions on formal mental health
services might be viewed as contradictory to their belief system. The beliefs of health
outcomes being predetermined, whether by curses in the family or by an act of supreme
power, also brought about delay in access to care due to the futility associated with
healthcare use (Olukotun et al., 2019). Preventative medicine, pharmacological solutions,
et cetera were thus viewed as supplementary to religious practices which are not clearly
defined (see Sackey-Ansah, 2021; Omenka et al., 2020).
Perceived Etiology of Mental Health Illnesses. Some diseases and health
imperfections, especially mental illness, were also viewed as consequences of human
inadequacies because of sin, cursing, prayerlessness, or as a God-ordained timeline for an
individual to teach him something in Christian, Islam, and indigenous religions among
African immigrants on multiple studies (Ndaita, 2018; Omenka et al., 2020;
SackeyAnsah, 2021; Saasa, 2019). This belief has been found to influence reactions
towards diseases management and health-seeking behaviors as first-line defense is
tackling the etiology of the disease. Traditional healers, exorcism, animal sacrifices,
repentance are reported to be the first line of treatment with medical care as a last resort,
thus delayed care in African countries (Sackey-Ansah, 2021). The delay in care was
consistent with studies in the United States involving black Americans not differentiated
from their origin with access and use of mental health care, where those accessing care
have a greater severity and chronicity from delayed care (MHA, 2020; Wharton et al.,
2018). Discrimination and Shame. Discrimination also affects mental health

care use among African immigrants. Nkimbeng et al. (2021), in a descriptive study
exploring experiences of discrimination and impact on health care use, found that African
immigrants experienced microaggression. Perceptions of microaggression were attributed
to their African accents, and the perceived discrimination was associated with poor
physical and mental health from reduced or delayed health care use (Nkimbeng et al.,
2021). The associations of perceived discrimination and poor mental health outcomes
were also consistent with studies done by Brown et al. (2018). Older, black African
immigrants reported more discrimination due to lower health care literacy, language
deficiencies, and lack of translators (Nkimbeng et al., 2021).
Lower use of mental health services were also noted among second-generation
African immigrants, where the children are American-born to African immigrant parents
(see Echeverria-Estrada & Batalova, 2019, Escamilla & Saasa, 2020; Obideyi &
Sangmin, 2021). Obideyi and Sangmin's (2021) findings in a longitudinal survey of 104
African immigrants found lower use of mental health services among second-generation
children or immigrant children due to their parent's reluctance to such care despite access
to mental health services in schools. The study was consistent with the results of
Echeverria-Estrada and Batalova (2019), which found that the ingrained beliefs from
parents transfer to their children; thus, children also viewed mental illness as an anomaly
and not a disease that needed treatment, leading to lower mental health care use. In 1st and
2nd generation African immigrants, perceived discrimination was noted to cause a delay in
access and use of mental health care, especially among African immigrant men who
report feelings of emasculation from discrimination, therefore preference not to seek

formal care (Escamilla & Saasa, 2020). The issue penetrates the African immigrants
despite education levels where Olokotun et al. (2019) determined in an explorative study
using semi-structured interviews that educated parents were more likely to use mental
health services for their children but less likely to disclose information to other African
immigrants. This was found to be a result of thoughts of shame of having a mentally ill
child, disgrace, and further isolation from their communities, a phenomenon noted by
multiple researchers (see Ekwonye et al., 2021; Olokotun et al., 2019; Omenka et al.,
2020; Ting & Panchanadeswaran, 2016; Wharton et al., 2018;).
An elevated level of shame on families with mental illness, shunning from
communities, and isolation leads to a lack of mental health care use among this
population group in young immigrants (Nantwi et al., 2017) and middle-aged immigrants
(Echeverria-Estrada, & Batalova, 2019) with worse outcomes in older immigrants who
have more barriers including language, illiteracy, and socioeconomic status (Agyekum &
Newbold, 2016). Results of a cross-sectional survey of 409 African Immigrants in the
United States represented from 31 African countries found that although exacerbating
factors of mental illness remains high from the pressures of acculturation, language
barriers, discrimination, and cultural acceptance of gender violence, the mistrust of health
professionals/western medicine and fear of shame in the communities create barriers to
seek care (Escamilla & Saasa, 2020). In a larger-scale study of 1,908 African immigrants,
Brown et al. (2018) reports a prevalence of perceived discrimination and psychological
distress, yet only 10% of African immigrants seek mental health care. These numbers are

consistent with African Americans' mental health care use in the United States (National
Institute of Mental health, 2020, Wharton et al., 2018).
Views on Preventative Care. Prevention is also frowned upon due to multiple
beliefs about diseases being a bad omen, a curse, a result of spoken word, and a
collectivistic culture where it is considered taboo to speak about ailments. Freeland et al.
(2020) noted that practicing active prevention of diseases or screening brought about
negative feelings and reduced quality of life with a feeling of not wanting to know about
their health among the participants. The belief of death is also considered the expiration
of one's life on earth, which is predetermined, hence posits that even with medical
intervention, God has ultimate control (Freeland et al., 2020; Sackey-Ansah,2021). As a
result, there are perspectives of futility viewed when dealing with diseases which also
leads to delayed health-seeking and lack of health service use.
Perceived Overdiagnosis. Overdiagnosis was a common ideology in describing
western medicine among African Immigrants (see eFreeland et al., 2020; Ludwig &
Reed, 2016; Payne & Hays, 2016). Ludwig and Reed (2016), in assessing views of health
care use among African immigrants using a framework thematic analysis, reported
findings of immigrants feeling ‘over diagnosed’ in the United States with statements like
“when you are here, you have hypertension, diabetes, and cholesterol.” The views of
overdiagnosis wase attributed to access to preventative health care but ended up with a
negative connotation on the immigrants with fear that accessing health care was equitable
with being labeled with diseases (Ludwig & Reed, 2016).

Preferences in Health Care Services. Results of an ethnographic study of 68
African Immigrants residing in New York on their views for health and access to health
services by Ludwig and Reed (2016) indicated that those seeking mental health services
preferred ethnic clinics that integrate spirituality and religion with western medicine. The
study also noted that mental illness was more prevalent among refugees arriving from
war-torn countries with no social support system and language barriers as they
acculturated to the dominant culture compared to voluntary immigrants, which were
similar findings to Ojikutu et al. (2018) and Panattiere et al., 2017. Still, Senreich et al.
(2016), through focus groups, considered the assistance offered to African refugees upon
immigration to the United States. They noted reliance on religion, marijuana abuse, and
lack of comprehensive culturally inclined mental health services to utilize after their
immediate settlement in their new habitation leading to more isolation and thus higher
reports of depression anxiety, and mental illnesses. The findings from the study also
showed a lack of familiarity with mental health services among African Immigrants due
to the lack of those services in their home countries, thus a less likelihood of their use in
the United States despite their accessibility (Senreich et al., 2016).
Mental Health Providers and African Immigrants
In an explorative listening study of psychiatrists examining their opinions and
experiences dealing with African immigrants’ mental illnesses, BeLue et al. (2021)
findings noted that all psychiatrists (N=8) felt ill-equipped to deal with the cultural
inferences among African immigrants. They voiced not feeling well prepared for
culturally responsive care needed for the immigrants (BeLue et al., 2021). National

Alliance on Mental Illness [NAMI] (2021) reported that there was a great need for
culturally competent mental health providers in the United States, especially when
dealing with the black population, who were more likely to describe physical symptoms
as related to mental health issues such as body aches when reporting depression. Lack of
cultural awareness with a conscious or unconscious bias towards black Americans who
include African immigrants, may thus lead to misdiagnosis and inadequate treatment (see
NAMI, 2021). BeLue et al., (2021) findings also noted the difficulties experienced by
psychiatrists providing care to African immigrants included mistrust of the systems of
care, the stigma of being labeled as crazy where some would accept taking an
antidepressant for pain but not for depression. Mistrust of interpreters or translators who
spoke African dialects rather than focus on mental illness being a priority to the African
immigrants were also listed as challenges for these providers.
Olukotun et al. (2019) reiterated the need for cultural and religious competence
among mental health practitioners in dealing with African immigrants rather than
grouping African immigrants as "black." Similarly, Omenka et al. (2020) noted that
grouping African immigrants as black, though phenotypically like African Americans,
produces erroneous assumptions in their care due to different health outcomes such as
lower cardiovascular risks, higher birth weights than African Americans. There is little
data on African immigrants' mental health, health care use, or long-term care in the
United States. The lack of studies focused on individual migrant groups like African
immigrants where providers can expand their knowledge base can thus relate to the lack
of cultural competence among the health providers.

Acculturation
Acculturation can be described as the cultural and emotional vicissitudes when a
minority culture interacts with a dominant culture (Agbemenu, 2016). Dominant cultures
are the cultures that are a majority in a specific region. As such, in the United States the
African immigrant's culture would be the minority culture, whereas the American culture
would be the dominant culture (Agbemenu, 2016; Freeland et al., 2020; Shoup et al.,
2020). Acculturation affects health choices, health-seeking behaviors, and health
outcomes (see Agbemenu, 2016; Ekwonye et al., 2021; Habecker, 2017; Freeland et al.,
2020, Nantwi et al., 2017; Omenka et al., 2020; Saasa, 2019; Shoup et al., 2020). The
effects noted are dependent on various factors such as nativity (Shoup et al., 2020),
proficiency in the English language (Nantwi et al., 2017), length of stay in the new region
(Agbemenu, 2016), age at immigration, educational level, socioeconomic status
(Freeland et al., 2020), and cultural attitudes (Habecker. 2017)
The main categories of African immigrants to the United States are either
francophone immigrants who are likely from French-speaking countries, coming to the
United States through refugee status, more likely to be Islamic, having less English
proficiency as compared to Anglophones who are more likely to be English speaking,
more likely to be Christians and more likely voluntary immigrants (Shoup et al., 2020).
Longitudinal studies (see Shoup et al., 2020) and exploratory observational studies (see
Habecker, 2017) determined that Anglophone were more enculturated, with a more
extensive support system through family unification programs and religious activities.
Thus, had better health access and consequently better health outcomes. Francophones,

on the other hand, were noted to have less support due to lack of access to social and
religious support from fewer mosques in places of settlement, less access to care due to
language barriers and health illiteracy, and had fewer reunification programs resulting in
more isolation (see Habecker, 2017; Shoup et al., 2020).
Despite trying to acculturate, some immigrants faced identity confusion where
they did not view themselves as full Africans or African Americans. Multiple authors
noted that the lack of studies on African immigrants regarding their identity, health risks,
health care preferences also contributed to identity confusion (see Ekwonye et al., 2021;
Omenka et al., 2020; Shoup et al., 2020; Saasa, 2019). In Ekwonye et al.’s (2021) study
of African immigrants, all participants reported confusion in completing medical forms
where the black category is not clearly defined, leading to African American, African
immigrants, Hispanic blacks, Indian blacks either reporting to be ‘black’ or ‘other’
category. The lack of specificity thus created a form of identity confusion, where African
immigrants almost always chose the black category despite feeling it did not adequately
describe them.
The age at the time of immigration is also an essential factor in health care use
and should be considered in treatment. In a longitudinal study of 482 African immigrants
aged 20 to 65, enculturation was found to be protective against cardiovascular risks due
to the increased social and collectivistic culture of African culture, which limited the
likelihood of adoption of adverse risk factors such as smoking and drinking among
immigrants coming to the country before they were 20 years old (Shoup et al., 2020).
Habecker (2017), through an observational study of African immigrants (N=37), showed

that immigrants did not leave their religious and cultural beliefs and experiences behind
after immigrating and were likely to carry the beliefs in their new region.
Interviews on adolescents, families, and parents from a mix of 17 African countries in a
Lutheran church noted that despite the number of years they had spent in the United
States, 75% still identified themselves as Africans, including 50% of adolescents who
came to the country as young children. The adolescents considered themselves Africans
but considered themselves “too white” for African Americans and “too black” for
Caucasians. The adults who represented 70% of the participants expressed feeling most
comfortable eating African foods, wearing African clothes, and speaking in their dialects
but felt they had to switch to “American ways” to be more easily understood at work or
social places (see Habecker, 2017). Shoup et al. (2020) also noted similar trends of
Habecker's (2017) enculturation among older and younger African first-generation
immigrants who were the first African-born family members to gain permanent residency
in the United States.
Theoretical Foundation
The Theory of Reasoned Action was developed in 1970 by Ajzen and Fishbein
(Ajzen, 1985). The construct of behavioral control was later added, and the theory was
refined to form TPB in 1980 (Ajzen, 1985; Boslaugh, 2019). TPB is a cognitive theory
used to predict and understand an individual's intention to perform a particular behavior
through understanding the relationship between human behavior and motivation
(Boslaugh, 2019; LaMorte, 2019). The theory has been successfully used to predict health

behaviors such as health care use, smoking cessation, drinking, drug abuse, medication
compliance, et cetera (Boslaugh, 2019).
Constructs of TPB
There are several constructs of the TPB (Boslaugh, 2019; Lamorte, 2019).
1) Behavioral beliefs are the individual insights and opinions that certain behaviors
would produce specific outcomes. These beliefs influence the attitudes towards
performing behaviors based on whether the outcomes are positive or negative;
hence if outcomes are perceived as negative, the attitude towards the behavior is
negative (Boslaugh, 2019; Vaismoradi et al., 2016).
2) Normative beliefs are the behavioral expectations from a group, such as friends,
family, or cultural groups (Asare, 2015; Boslaugh, 2019). The normative beliefs
influence the individual beliefs due to pressures to conform with the group
beliefs. There is less pressure when an individual behaves in a way that conforms
with group behavior than when they act oppositely.
3) Control beliefs are the factors that hinder or accelerate an individual in
performing a behavior. When an individual perceives difficulty in performing a
behavior, they are less likely to perform than when they have ease in performing
it (Boslaugh, 2019; LaMorte, 2019)
4) Actual behavioral control is the true extent of performing the behavior using
resources and skills needed to complete the behavior
Figure 1
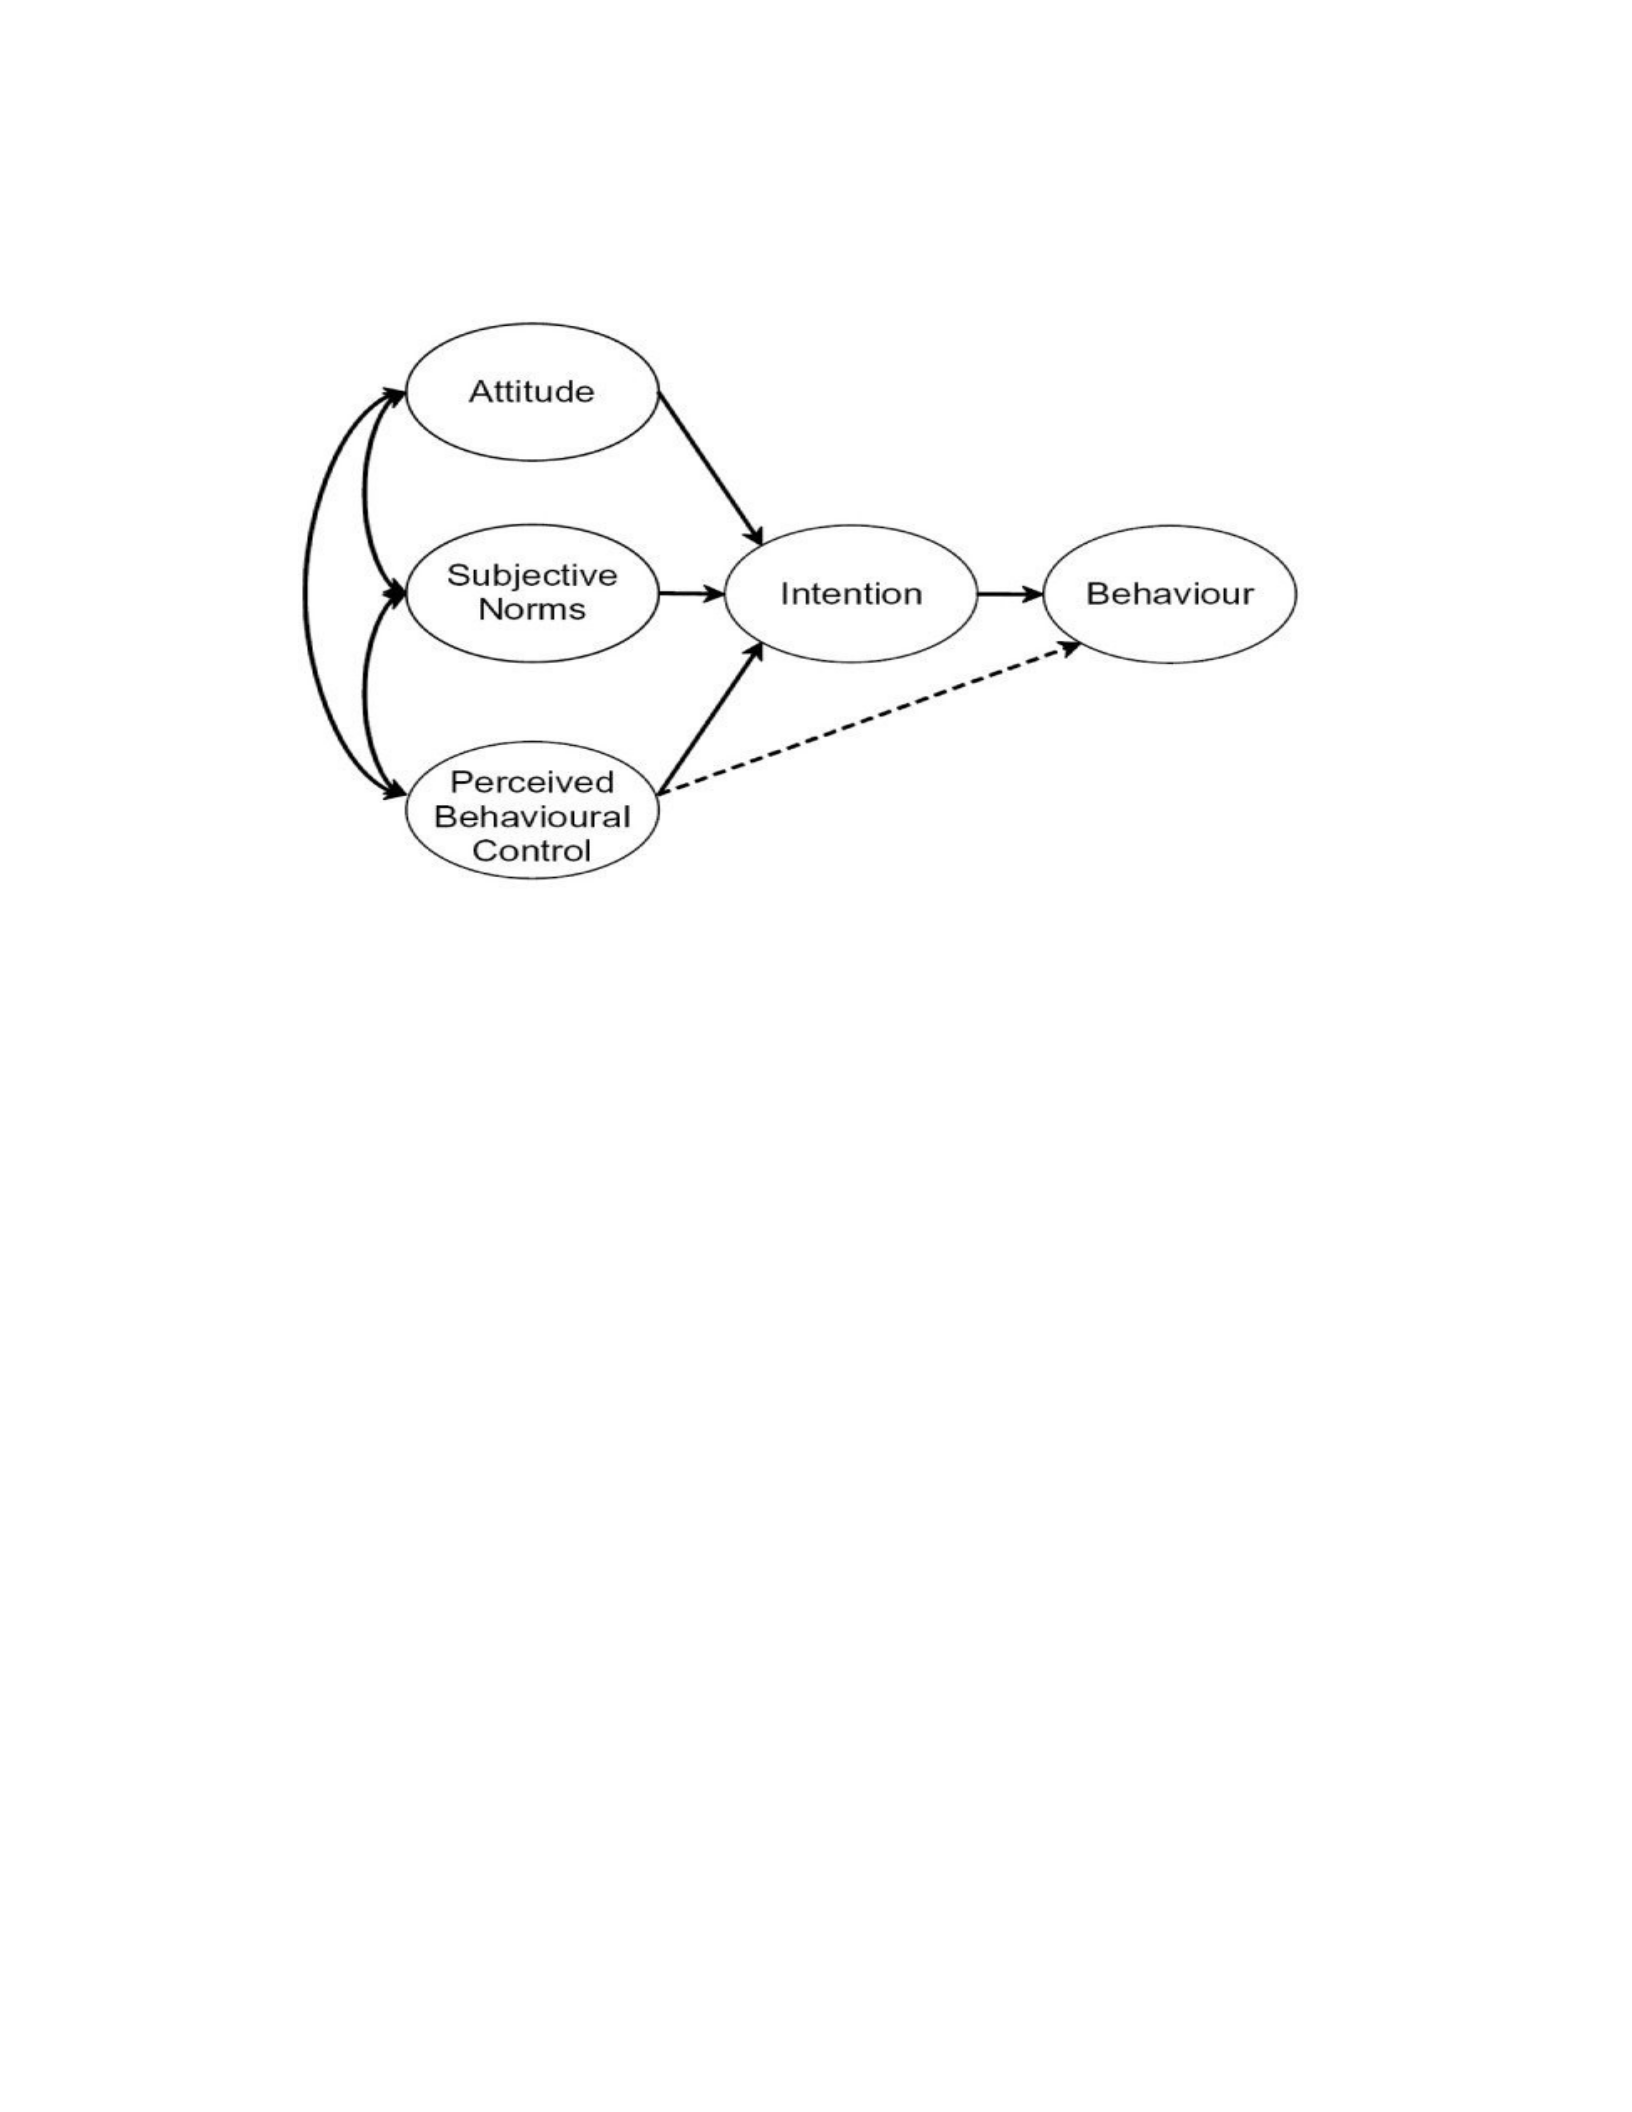
Theory of Planned Behavior
From “Factors influencing the use of public dental services: An application of the Theory
of Planned Behaviour” by L. Luzzi, & A. Spencer, 2008, BMC Health Services Research,
8(1), P. 93.
Assumptions
TPB assumes a straightforward or linear executive process from the intent to the
actual behavior; thus, it does not account for changes that occur with time, such as
acculturation of immigrants in the United States (LaMorte, 2019). The theory also
assumes that all individuals would have the same resources, opportunities, or health
services access to perform certain behaviors (LaMorte, 2019). As noted, immigrants have
varied opportunities depending on many factors, including the reason for immigration,
education level, and family presence in the United States (Shoupe et al., 2020). Other
variables such as fear, past experiences are not accounted for in behavioral intention and
the period between the intent and action is also not addressed; thus, it would be unclear

how long the theory would be useful in predicting certain behaviors (Boslaugh, 2019).
The period between intent and action is essential since mental illness may limit the
cognitive drive to access help from feelings of helplessness and hopelessness; thus, their
behavior prediction is not as linear as TPB would expect it to be (MHA, 2020; Shoupe et
al., 2020).
Application of Theory to Constructs of Study and Relation to Study
TPB posits that attitude towards behavior, perceived behavioral control, and
subjective norms, derived from the primary constructs of behavioral, normative, and
control beliefs, are the main themes that influence behavior patterns (Asare, 2015;
Boslaugh, 2019; LaMorte, 2019; Tornikoski & Maalaoui, 2019; Vaismoradi et al., 2016).
Using the themes of TPB allows thematic analysis for both latent and manifest content,
with coding being completed through probable subthemes for this qualitative study on
understanding the influence of religion on mental health use on African immigrants in the
United States.
Behavioral intentions are motivational factors influencing behavior; thus, the
more robust the intention, the more likely the behavior's engagement (Asare, 2015).
Understanding the role of religion in mental health care use is essential in fully
understanding the motivational factors that would lead to more African immigrants
seeking mental health care help. Capitalizing on these motivational factors can thus
predict positive behavior among African immigrants, according to TPB (Boslaugh, 2019).
Behavioral intentions among African immigrants are essential in understanding their
experiences with mental health care use. If their motivational factors remain low such as

lack of culturally competent health care providers (Ekwonye et al., 2021), lack of mental
health knowledgeable clergy (Payne & Hays, 2016), or language barriers (Omenka et al.,
2020), then their intentions remain low and consequently increase lack of mental health
use both formally in clinics as well as in their religious institutions. The attitudes
towards behavior are the favorable or unfavorable appraisal from the behavior and
comprise behavioral beliefs and outcome evaluations. Positive attitudes from a religious
perspective are consequently fundamental to understand as multiple authors findings
concur that the African immigrants first-line source of help is less likely to be formal
mental health care and more likely to be religion (Adu-Boahene et al., 2017; Echeverria-
Estrada & Batalova, 2019; Ekwonye et al., 2021). The positive attitudes can then be used
to foster more engagement in the desired help-seeking behavior. If the appraisal is
unfavorable, engagement would be unlikely in the behavior (MonnapolaMazabane et al.,
2021).
The subjective norm is the social pressure to perform or not to perform a specific
behavior. The subjective norms in religion among African immigrants to be discovered
through the research would provide a greater understanding of the role of religion in
mental health care use. These norms can be used to used positively to enhance
community participation to increase behavioral intention, thus increasing mental health
care use. This construct is vital in immigrant societies due to the value of community
support (Agbemenu, 2016; Asare, 2015; Ojikutu et al., 2018; Omenka et al., 2020;
Wharton et al., 2018). Behavioral control or the ease or difficulty of performing behavior
can also be understood in the study; hence future interventions of reducing if not

eradicating the barriers can be implemented by the religious organizations and health care
providers to increase health-seeking behaviors (Asare, 2015; Vaismoradi et al., 2016).
TPB will thus assist the researcher in understanding how religion among African
immigrants interacts to facilitate or hinder mental health care use.
Literature Analysis on Use of Theory
Berkley-Patton et al. (2019), in a longitudinal study, used TPB and
communitybased participatory research to collaborate with the black church to foster HIV
testing interventions and found that there was an increase in HIV testing in church-based
testing relative to controls. The stigma associated with AIDS/HIV among the black
community has been linked to reduced healthcare use rates; thus, Berkley-Patton et al.
(2019) tested the feasibility of HIV testing outcomes of Taking It to the Pews (TIPS), a
multilevel HIV education and testing intervention. The constructs of HPB were tested at
monthly intervals and included the intention of HIV testing in the church, attitude about
church testing, perceived norms about HIV communication in the church through
sermons or bulletins, and perceived behavioral control of whether participants could test
for HIV in the church. Testing noted increased HIV testing in the church at six months,
which correlated with increased intention to test, positive attitude of testing benefits,
increased norms of discussing HIV in the church, and the perceived behavioral control of
the intent to go ahead to test.
Lefevor et al. (2020), in a multilevel modeling study of 298 participants from 20
congregations across Islam, Christianity and Judaism, examined individual and
congregational factors that played a role in psychotherapy-seeking behaviors. The

primary constructs studied in TPB were attitudes to seeking treatment and subjective
norms beliefs around seeking psychotherapy. They found that increased scripture reading,
and service attendance were negatively correlated with help-seeking behaviors.
Religiousness thus influenced therapy seeking through influencing attitudes towards
seeking treatment, norms, and perceived behavioral control of psychotherapy. The
panegyrization of mental health by religious leaders may encourage help-seeking through
changing attitudes and norms hence increasing the perceived behavioral control towards
mental health care services.
Taylor et al. (2019) mirrored Lefevor et al. (2020) in finding that the TPB in
research successfully demonstrated the various factors contributing to the underutilization
of psychological help among African Americans. TPB was utilized in their study to
examine perceived negative outcomes associated with seeking care, such as stigma and
shunning from communities, which reduces the likelihood of the behavioral intention.
The social pressures such as endorsement of beliefs that black people do not get
depressed, do not seek help, must be strong, or that seeking mental services means one
has a weak prayer life increases the subjective norms, which in turn reduces the intention
of health-seeking behaviors (Taylor et al., 2019). The perceived difficulties of seeking
help such as microaggression, mistrust by health professionals, lack of culturally
competent providers, difficulties discussing race and ethnicity in therapy also contribute
to perceived behavioral control. When perceived difficulty is high, the attitudes are
negative, and the behavioral intention is low, thus increasing the underutilization of
mental health services (Taylor et al., 2019).

TPB research is not limited to mental health care use but also to preventative
screening services. Edelstein et al. (2020) studied the use of TPB in an ethnographic
study to screen for bone mineral density across multiple ethnic groups of one hundred
people each among Israeli-born Jews, Israeli-born Bedouin Muslims, and Jewish
immigrants from the former Soviet Union through face-to-face interviews. The former
Soviet Union immigrants had the lowest screening behavior and more robust religious
views, like Lefevor et al. (2020). Consequently, they noted lower scores on the TPB
constructs such as lower knowledge, negative attitudes to assessing, discouraging
subjective norms, and lower intentions to screening behavior. TPB can be used to
examine the numerous factors that contribute to lower healthcare use.
Summary
In this study, I seek to gain a deeper understanding of the role of religion in
mental health care uses among African immigrants. The significant themes noted in the
literature review from recent data are religion, mental health perceptions, acculturation,
mental health use, and stigma. Data from peer-reviewed journals indicate that religion
plays a role among African immigrants' mental health care use, but the way religion
impacts the use is not understood. Religion has been identified as an essential factor in
most studies examining the underusage of health care services; thus, studying the role of
religion in mental health-seeking behaviors is paramount in this migrant group. The
current study will examine the role of religion on mental health care use among African
immigrants using the constructs of the TPB such as attitudes, behavioral control, and
subjective norms. The use of qualitative ethnographic processes using semi-structured

interviews will hence provide more profound knowledge and understanding in filling this
identified gap.
Chapter 3: Research Method
The purpose of this study was to provide a qualitative exploration and
understanding of the impact of religion on mental health care use among African
immigrants in the United States. The information gained from this study built on
available literature on African immigrants in the United States to inform clinical care on
management of African immigrants' mental health with the aim at an overall
improvement in the quality of care received by African immigrants regarding their mental
health, thus improving their quality of life. This chapter will describe the research design,
rationale, the population, data collection procedures, the role of the researcher, explain
the methodology with instrumentation, data analysis plan as well as discuss issues of
trustworthiness and ethical considerations
Research Design and Rationale
The purpose of this study was to understand the role and impact of religion in
mental health care use among African immigrants in the United States. The following
research questions guided the study:
RQ1: What are the experiences of African immigrants in the United States with
mental health care use?
RQ2: How does religion influence mental health care use among African immigrants
in the United States?

The study was a qualitative in approach with an ethnographical research design.
Qualitative studies provide a deeper understanding of the subject, thus yielding in-depth
data about the community (Burkholder et al., 2016). Through ethnography, cultural
groups such as African immigrants in the United States are studied to understand their
characteristics and way of life. As such, the role of religion to African immigrants was
examined as it related to mental health care use in the United States. Ethnographic studies
examine people in their environment through various methods (Morgan-Trimmer &
Wood, 2016). I used semistructured interviews to get data and study the African
immigrant population in Houston, Texas.
Semistructured interviews provide a guide to ask questions but also provide
leeway for interviewers to probe for more data as well as allow the interviewee to provide
as much information as they need in detail, thus adding to the depth of the qualitative
research (Burkholder et al., 2016). The interviews occurred in the United States in the
natural settings/environments where participants live, work, or play, which is an essential
element in ethnographic qualitative studies (see Aspers & Corte, 2019). This element
helped me understand the lived experience of African immigrants in the United States
regarding their religion and mental health care use.
Ethnographic studies help understand cultural groups or subsets of populations
which helps decipher them and understand their way of life and their behaviors
(MorganTrimmer & Wood, 2016). My ethnographic study was instrumental in
understanding the fastest-growing immigrant group in the United States, African
immigrants, thus provided useful information regarding how religion impacts their mental

health care use, which inevitably improves their health outcomes by enabling health
providers and religious leaders to work together to improve mental health among African
immigrants in the
United States.
Role of the Researcher
As the researcher, I conducted all interviews using semistructured interviews,
which allowed me to obtain more information through a two-way communication where
not only the answers to the questions are answered, but also the reasons behind the
answers are prodded. Interviews were set up in natural, informal settings where they
lived, worked, or played to ensure the participants were comfortable and could provide
in-depth information. As the researcher and an African immigrant living in the United
States, I needed to exercise a lot of self-reflection using a reflexivity journal to ensure that
my thoughts and opinions were not reflected in the interviews or analysis of the study.
Regarding my role of being an African immigrant yet being the interviewer, Pessoa et al.
(2019) suggested that ignoring the social differences and social roles can produce an
oppressive research process where the interviewee feels their life experiences are the only
part of importance. As such, reflexivity was used where I could share my thoughts on my
role, thus exposing personal biases that may be present and integrating reciprocity into
the development of the knowledge acquired.
I did not have any professional or supervisory relationships with the participants
in the study that would involve power over the participants. To ensure this professional
relationship, I informed each interviewer of my role as a researcher and the need to

remain objective throughout the study. This was necessary to avoid any biases and to
ensure an open, honest interviewing process without any persuasion. The interview guide
used the why, what, where, how, and when questions to understand the meaning and
interpretation of their experiences.
Methodology
I used an ethnographic qualitative design to understand the role of religion on
mental health care use among African immigrants in the United States. An ethnographic
design allowed me to study the cultural group, which in this case was African
immigrants, in their natural settings to understand their behaviors and characteristics that
make them behave in a certain way, where in this case was the role of religion in mental
health care use (see Ravitch & Carl, 2016). Ethnographic researchers collect firsthand,
high-quality data, thus producing in-depth information about the cultural group being
studied (Morgan-Trimmer & Wood, 2016). I used semistructured interviews, which
allowed for more information rather than a rigid question and answer modality of
structured interviews. The interviews took place in a conversational mode which was
easier for the interviewee to divulge information and feel more comfortable with the
interview process.
Population
The population of interest was African immigrants residing in the United States
for at least 3 years since immigrating. Participants chosen had to have immigrated to the
United States as adults. The sample chosen was English-speaking and living in Houston,
Texas. I attempted to recruit from varied and multiple African countries to offer a

diversified ethnic background for the research. The participants were above 18 years old
with no preference in gender or occupation.
Sampling Strategy
Purposeful sampling strategies were employed in the research study. Purposeful
sampling is essential in qualitative studies to ensure that the participants provide the
specific data needed. Participants were carefully recruited to ensure they were African
immigrants who were legal immigrants in the United States, immigrated as adults and had
at least 3 years of residence in the United States, spoke English, and were above 18 years
of age. Purposive sampling ensured participants met the screening criteria hence it was an
appropriate strategy for an ethnographic qualitative study where a specific culture was
investigated (Ravitch & Carl, 2016). Qualitative studies do not have a set sample size,
and data saturation determines the sample sizes. Data saturation was described by
Creswell (2015) and Vasileiou et al. (2018) as the point in research where no new
information is discovered and the point where there is data redundancy. Data collection
continued until saturation was reached. Studies on data saturation have identified that in
inductive thematic analysis studies, approximately 80-90% of all concepts identified were
noted in the first 10-12 interviews (Guest et al., 2020; Francis et al., 2010; Namey et al.,
2016). I hence estimated about 10 participants to reach saturation.
Instrumentation
Semistructured interviews were used to investigate and gain a better
understanding of the phenomena of interest, which was the role of religion in mental

health care use. The interviews were also framed around the TPB and ethnographic
qualitative design. I focused on behaviors among African immigrants residing in the
United States Ravitch and Carl (2016) emphasized the need for interview questions to
align with the research question to ensure that the research questions are answered, and
methodology is followed. The interviews questions were framed around understanding
mental health perception among African immigrants and understanding the role of
religion in their everyday lives. All questions were descriptive, open-ended, neutral, and
non-leading to elicit a more in-depth information base (see Patton, 2015). I developed all
the interview questions using TPB to provoke the theoretical concepts discussed in
Boslaugh (2019). The interview guide is attached in Appendix B.
Journal notes during the interview, as well as observation during the interviews,
provided a varied data collection method and triangulation. Journal notes were essential
for analysis using a summative approach as they provided more interpretive data (see
Ravitch & Carl, 2016). Observation of nonverbal cues such as hesitation, laughter, and
facial expressions enabled me to probe for the thoughts behind the reactions, thus
enriching the data at hand.
Procedures for Recruitment, Participation, and Data Collection
I posted fliers (see Appendix A) in local African places of worship such as
churches and mosques, African restaurants, and local African shops where African
immigrants purchase African foods. These areas also served as meeting places for many
Africans thus were appropriate to reach the desired population for the study. The fliers
contained my contact information, the reason for the study, and the topic of the study. I

identified local Christian leaders and Muslim leaders to determine if they were willing to
have fliers posted in their places of worship to recruit participants. I also used a
snowballing method by asking recruited participants to pass along my contact
information to other people they knew who would be interested in the study.
All inclusion criteria were shared during the recruitment phase, where those who
met the criteria contacted me for the study. I ensured those chosen met the inclusion
criteria by asking again the criteria questions in the flier once they contacted me with
their interest to participate in the study. I chose the first 10 participants who meet the
inclusion criteria and scheduled the interviews. I emailed the consent form to each
participant and requested their consent to undertake the interview. The informed consent
forms provided a brief description of the study, discussed its purpose, procedures, risks,
and benefits. Confidentiality and privacy issues were communicated to ensure the
participants knew that all information would be protected throughout the study. I made
participants aware of free community resources available to them if concerns or
potentially triggering points came up in the interview. The time commitment of about 60
minutes was also communicated for participant preparation before the study.
Data collection began after Walden University Institutional Review Board (IRB)
approval (approval number 05-20-22-0986249). Individual face-to-face interviews were
arranged. Due to COVID 19 pandemic, virtual meetings were an alternative optional
method. This option was communicated ahead of time while scheduling the interviews.
Virtual visit included Zoom which allowed for observation of facial expressions to be
noted by the interviewer. I provided an option for face masks for the in-person interviews

and disclosed my COVID vaccination status. All interviews irrespective of in-person or
virtual were be audiotaped, and field journal notes were taken during the interviews.
Interviews lasted approximately 60 minutes each. The interviews took place in a centrally
located library conference room that I booked ahead of time to provide a safe and neutral
space for data collection. An alternative location was arranged in the case that the library
conference room was not available. The interviews were then conducted by beginning
with a brief demographic survey (Appendix C) then followed by semi-structured
interviews. I provided closing statements to each participant and debriefed them after
collecting data. Debriefing was necessary for the participants to express their thoughts
regarding the interview and to offer a relaxed environment before they left the conference
room or the Zoom space. The audio recordings and journal notes were stored in a
password-protected personal computer for safekeeping. Each participant was
compensated after the interview with a twenty-dollar local restaurant gift card. Data
collected were then transcribed through Zoom transcription services. Upon transcription,
I offered participants a chance to review the typed transcripts for accuracy of the
interview. I then coded and analyzed data to identify emerging themes
Data Analysis Plan
The purpose of the study is to understand the role of religion in mental health use
among African immigrants in the United States. After data collection, the recorded audio
from the interviews was transcribed into a word document. The fields notes and
observations were also analyzed manually as they provided richer data collected during
the interviews that may not have been recorded such as grunts, smiles, sadness, smirks et

cetera. I first typed up the preliminary field notes then manually coded them using a
deductive approach. After transcribing the recordings, codes were derived and aligned to
the research questions. I utilized thematic analysis to search for differences and
similarities within the data collected, thus summarizing the data into information that
could answer the research question. Thematic analysis was developed by Braun and
Clarke as a reliable way of qualitative data analysis that involves interview transcripts;
thus, it was an appropriate analysis method for this study (Braun & Clarke, 2014).
Thematic analysis involves a systematic process:
1. Familiarization with the raw data through transcribing and reading
journal notes
2. Coding of the data
3. Generating themes
4. Reviewing themes
5. Defining and naming themes
6. Write up
A deductive approach based on the TPB with a semantic approach was utilized.
The semantic approach required analyzing the content rather than the assumptions of the
underlying data. I employed manual coding to control and maintain ownership of my
work. Parameswaran et al. (2020) states that coding breaks down qualitative data into
meaningful phrases that help make sense of the vast data. I chose to use Dedoose
software as a qualitative analysis software due to ease of use, cost, transferability,
transcription, analysis potency, visualization, data mapping, and privacy maintained by

the software. The software thus enhanced coding and theme categorization. The codes
were then grouped into categories that formed emerging themes guided by TPB. All
themes were categorized and stored in a password-protected memory card for safe record-
keeping.
Issues of Trustworthiness
Trustworthiness is critical in qualitative research as it indicates the authenticity of
the study through examining factors such as dependability, credibility, conformability,
and transferability (Burkholder et al., 2016; Elo et al., 2014).
Credibility
Leung (2015) describes credibility as the extent to which a study can be believable
hence meaning that the data provided can confirm the study. It is hence the measure of
honesty and accuracy of the data to establish that it is true. It checks the study's internal
validity by how well the research represents the phenomenon studied. To ensure the
study's credibility, I utilized member checking, peer debriefing, and triangulation.
Member checking involved returning the results and transcripts of the data
collected to the participants to ensure information was accurate and resonated with the
information they provided. Member checking ensured high-quality data (Ravitch & Carl,
2016). Triangulation uses multiple approaches to answer the research question (Ravitch
& Carl, 2016). It was achieved through varied ways of data collection where information
was audiotaped, journal notes were taken, and observation was conducted during the
interviews. Peer debriefing was utilized to establish credibility. Peer debriefing involved
using an unbiased and independent peer to enhance the validity of the research. This was

achieved through my dissertation committee reviewing all the work presented throughout
the research process.
Transferability
Burkholder et al. (2016) describe transferability as a measure of external validity
in research that examines the extent to which the results of a qualitative study can be
generalized to other settings. Given the scant data of African immigrants and their mental
health, I ensured that a detailed, in-depth description was provided regarding the
background, project details, methods, findings, assumptions, processes, and outcomes.
Elo et al. (2015) posit that the more information provided, the better the study
transferability. Participants’ descriptions, sample selection, analysis is also needed to
offer a more detailed description of the study that enhances transferability.
Dependability
Dependability is the process of ensuring that data remains stable over time, thus
ensuring the consistency of data collected, analysis, and reporting in the entire study
(Burkholder et al., 2016). Burkholder et el. (2016) reports that dependability is essential
in providing reliability and consistency in the research. To ensure such stability, I used
triangulation in data collection. Triangulation was ensured through multiple data
collection methods, from audio recordings to journal notes and observations, ensuring
that the information collected was stable and consistent.
Confirmability
Confirmability ensures that other researchers can verify the study and that the
level of confidence in the study is based on participants' narratives rather than researchers'

opinions (Ravitch & Carl, 2016). To maintain conformability in this study, a reflexivity
journal was used and maintained throughout the entire study in which I reflected on what
happened and record all values and interests of the study. Leung (2015) posits that
reflexive journals also ensure that a researcher can acknowledge the process, biases, or
any opinion that may affect their objectivity in the project, thus ensuring the validity of
the data.
Summary
I used a qualitative design to understand the role of religion in mental health care
use among African immigrants living in the United States. The purpose of this study was
to provide an explorative understanding of mental health use among African immigrants
concerning their religious practices. Information from this study provided more data
regarding African immigrant health, thus improving the quality of mental health care
received, overall wellness, and reduced disparities among minority groups which
produces a positive social change to African immigrants in the United States.
An ethnographic study was conducted using TPB as the guiding framework using
semi-structured interviews to ensure in-depth enriched information collection from 10
carefully selected participants through purposeful participant selection. Informed consent
was provided to ensure that participation was purely voluntary and to outline the
expectations of the study. Data was audio recorded, and journal notes were taken during
the interview while maintaining the privacy and confidentiality of the participants. All
participants were debriefed after the interview. The data collected was analyzed through
thematic analysis to derive codes and themes. Dedoose software was used to assist with

data analysis. To maintain credibility through the study, a reflexivity journal was kept and
maintained, triangulation in data collection was verified, and transcripts/results were
checked with participants to ensure the accuracy of the data provided. The next chapter
will discuss the findings and study results.
Chapter 4: Results
The purpose of the qualitative study was to understand the experiences of African
immigrants in the United States with the mental health system and understand how
religion influences mental health care use among African immigrants. I used open-ended,
semistructured questions to interview 10 participants for the study. The open-ended
questions provided in-depth answers to the questions which were all used to answer the
two main research questions. The interviews were all in person and each lasted about 60
minutes. The following research questions were used in this study:
RQ1: What are the experiences of African immigrants in the United States with
mental health care use?
RQ2: How does religion influence mental health care use among African
immigrants in the United States?
This chapter will describe the setting, demographics, data collection procedures, thematic
data analysis, evidence of trustworthiness, reporting of the data analysis, a summary of
the emerging themes that arose from the data and provide a summary of the whole
chapter.

Setting
Approximately 100 fliers were distributed in African religious institutions,
restaurants, and shops in the Houston metropolitan area. Participants were recruited
through purposive sampling. Individuals interested in participation contacted me through
the information provided in the flier. Upon participant contact, eligibility was determined
through inclusion criteria, 10 participants met inclusion criteria and were recruited for the
study, and interviews were scheduled. Participants were offered the choice to schedule
face-to-face or virtual interviews using the videoconferencing tool Zoom (2022). Five
participants choose the virtual option while the other five choose in-person interviews.
Semistructured interviews occurred on various dates over 2 weeks from May 21st to June
2nd, 2022. All in-person interviews were held in the conference room of a local library.
The conference room was private and only the participant and I were present. There were
no interruptions during the interviews. Each in-person interview was audio recorded
using a Zoom audio recorder. The virtual interviews were conducted from my home using
Zoom. I used Zoom for audio and transcript recording data for both in-person and virtual
interviews.
Data Collection
Data collection began after IRB approval was received and took approximately
two weeks. Five participants chose virtual interviews over in-person of fears of Covid-19
as well as convenience. All participants were from the Houston metropolitan area and
interviews were conducted in English as outlined in the recruitment flier and consent
form. Participants provided consent via email before the interviews. Data were collected

from a total of ten participants. The obtained data was qualitative using the interview
guide (Appendix B) with deeper probing and follow-up questions employed when
necessary. For the in-person interviews, I used the Zoom phone application to audio
record which also provided the verbatim transcripts while for the virtual interviews,
Zoom was also used for both audio and transcription services. Most interviews lasted
approximately 60 minutes however, three interviews lasted approximately 80 minutes as
participants wanted to “talk some more”. Saturation was noted on the eighth interview,
but I continued with two more interviews to ensure no new information was emerging.
Journal notes were taken during the interviews where emerging codes and observations
were noted. At the conclusion of each interview, I listened to the audio recordings and
reviewed the transcripts from Zoom which had a lot of inconsistencies due to the various
accents and pronunciations, and made corrections as needed. There was however no
language barriers or misinterpretation of any questions during the interviews. I then
emailed each participant’s transcript to them to review for accuracy. None of the
transcripts were changed or edited by the participants. I went through each audio
recording, transcript, and journal notes again to gain a deeper understanding of the
content. All data were stored on a password-protected computer to which only I have
access. Data collection went according to plan without any variations or deviations from
the methods described in Chapter 3.
Demographics
Participation was limited to African immigrants living in the United States who
had immigrated to the United States as adults and had lived in the United States for at

least 3 years. Table 1 presents the demographic classifications of the participants which
include geographic African place of origin, age range, income range, education level,
religious affiliation, and the number of years residing in the United States. Most
respondents came from East Africa (N=5), South Africa (N=3), and with fewer
participants from West Africa (N=2). I did not have any recruited participants from
northern Africa. Most of the participants earned above $80,000 annually, had an
undergraduate degree, and were in the 41-50 age range. There was equal distribution
between males and females.
In terms of religion, a majority (N=6) were protestant, and the remainder were
non-denominational (N=3), and Catholic (N=1). Figure 2 shows the distribution
respondents by African region. Fifty percent of the respondents were males while the
other 50.0% were females. Further, most of them had above an undergraduate level of
education (N=8).
Table 1
Demographic Data
Participant Gender Age Country
Years in
United
States
Religious
affiliation Education Income
P1 Female 40-49 West
Africa 21-30 Protestant Graduate $80, 000<
P2 Female 40-49 West
Africa 21-30 Catholic Graduate $80, 000<
P3 Female 40-49 East Africa 21-30 Protestant Graduate $80, 000<
P4 Male 50-59 South
Africa 21-30 Protestant College $40,000
$80,000
P5 Male 40-49 East Africa 21-30 Protestant Undergradu
ate $80, 000<
P6 Male 40-49 East Africa 21-30 Nondenomi Undergradu $80, 000<

national ate
P7 Female 30-39 East Africa 11-20 Nondenomi
national
Postgraduat
e $80. 000<
P8 Female 40-49 South
Africa 3-10 Protestant College $40, 000
$80, 000
P9 Male 40-49 South
Africa 11-20 Protestant Undergradu
ate
$40, 000-
$80, 000
P10 Male 40-49 East Africa 21-30 Nondenomi
national Graduate $80, 000<
Figure 2
Distribution of Respondents by Region
Data Analysis
The purpose of the study was to understand the role of religion in mental health
use among African immigrants in the United States. After data collection and proofing of
all transcripts, I saved the note form of the transcripts from Zoom into a Microsoft Word
document. I then printed out all the interview transcripts and color-coded the responses
according to each question in the interview guide. Responses to each question were
thoroughly evaluated to look for similarities and meaningful phrases. I used the actual
phrases rather than implied meaning to ensure that I remained as objective as possible to
what the participants were stating rather than what I thought it meant. I looked for
meaningful phrases for each individual participant and then looked for similarities in
5
32
0
2
4
6
East Africa South Africa West Africa

those across participants. Descriptive coding was used by summarizing content into a
descriptive word. This process resulted in 40 descriptive codes. According to
Parameswaran et al. (2020), coding is used to break down data into meaningful phrases.
Coding thus involved two stages to bring meaning to the raw data. The first initial round
was used as a summary to describe the quotes from the raw data then the second
deductive coding added an interpretative thematic analysis while answering the research
questions.
I then grouped the codes into categories that represented an underlying common
idea. The broader categories were then combined to form themes which were named
based on the key topics and were organized by research question. Ravitch and Carl
(2016) define themes as perceptions derived from research. I used thematic analysis to
make meaning of the derived perceptions to identify the interactions, associations, and
differences within the collected data, and to summarize the data into information that can
answer the research questions. The final themes were hence identified and determined
from classification of the categories based on responses and research questions.
I then used Dedoose (2022), a qualitative analysis software for further thematic
analyses and coding which also ensured further validity. Dedoose was useful in making
sure a thorough analysis was conducted. With Dedoose, I imported the cleaned-up word
documents into the software, one document for each participant. I then set up descriptor
data, a tag in the Dedoose software, with demographic data for each corresponding word
document and linked each descriptor data to the corresponding word data document
already uploaded. Demographic information included in the descriptor data were

presented in Table 1. Dedoose requires a thorough evaluation of the data to develop
codes. For this step I used the codes I identified during the manual coding process.
Analysis in Dedoose showed the frequency and weight of the codes which confirmed the
manual coding results. Since Dedoose relied on identified codes which I had already
identified in manual coding, there were no variances between the two methods and the
software allowed me to confirm the weight or frequency of the codes already identified.
Table 2 shows the organization of themes, categories and codes derived from the analysis
process.
Table 2
Organization of Themes, Categories, and Codes
Theme 1-Insight in mental
illness
Theme 2-Treatment of mental
illness
Theme 3-Role of religion
Category 1- Definitions of
mental illness
Category 5-Cultural influence
Category 10-Education
Category 2-Causes of mental
illness
Category 6-Religious influence Category 11-Normalization
Category 3-Cultural
inferences
Category 7-Disclosing mental
illness
Category 12-Collaboration
Category 4-Religious
inferences
Category 8-Formal mental
health perceptions
Category 9-Stigma and shame

Codes
-Curses
-Consequences of wrongdoing
-Demons
-Something is wrong with
mind
-Phobia to mental diagnosis
-Sadness
-Lunatic
-Demon possession
-Ancestral powers
-Inadequacies of religious
living
-familial origin
-shunning
Codes
-Traditional rituals
-pray and fast
-do good
-Sacrifice to ancestors
-Ignore -stigma
-not sharing
-hide disease/privacy
-Institutionalization
-sharing with non-Africans
-secrecy
-shunning
-racism
-discrimination
-stereotyping
-mind-altering medications
-side effects
-addiction
-not the same as other
medications
Codes
-remove stigma/talk more
-provide support
-education
-collaborate
-currently in adequate help
-not talked about
Thematic Analysis
This section will provide detailed results from the analysis. Three emerging
themes will be discussed with their 12 corresponding categories. I will discuss each
theme and its subsequent categories separately. The themes and categories were used to
answer the research questions for this study.
Theme 1: Insight on Mental Illness
The first theme was insight into mental illness. The theme emerged from the
questions in the interview guide asking about describing mental health, how mental
illness is viewed among African immigrants in faith settings, and the causes of mental
illness. Categories under this theme include a definition of mental illness, causes of
mental illness, cultural inferences of mental illness, and religious inferences of mental

illness. The theme answers the research question regarding the experiences of African
immigrants in the United States with mental health care use as well as how religion
influences mental health care use as noted through religious causes of mental illness.
Definition of Mental Illness
All participants answered the question about describing mental illness. Eight
participants reported that mental illness relates to “cognition, thinking, mind issues” and
they felt it touched on an individual’s “psychological and emotional functioning,” while
two participants felt they did not know much about mental illness and described it as
“antisocial behavior and lunacy” of individuals. P1 described mental illness as
“something that affects your emotional health” while P2 described it as “mental
instability”. All 10 participants mentioned in their description that there is much more
knowledge of mental illness in recent years in the media and they did not have this prior
information in their countries of origin. P3 stated “I have been here for more than 2
decades, and I have only learned about mental illness in the last 3 years”, P7 stated
“discussions about mental health are now happening but were not as public before”.
Participants in the United States for less than 10 years had more deficiency in knowledge
of the mental illness. P8 stated, “I am not sure what it is, isn’t that more of an American
term?”
Spiritual Inferences About Mental Illness
In terms of the feelings of the respondents about how African immigrants in faith
settings deal with mental issues, most of the respondents stated that persons with mental
issues are seen as “being demon possessed” and were looked at them as “weak Christians

who do not pray or fast enough” or “had a distant relationship with God.” All 10
participants stated mental illness is highly ignored in religious settings and not thought of
as a real problem, P5 stated “we just ignore it and do not talk about it, hoping it goes
away.” Half of the participants mentioned “casting out demons and exorcism” for mental
illness. P8 stated, “We pray and cast out the demons as well as have traditional rituals to
remove the demons” while P3 stated “If you are mentally ill, they think you are
demonpossessed. Something has come on you and you need demons to be cast out or you
need prayer or performing some kind of ritual.” Participants’ perceptions of mental health
are heavily shaped and informed by their religious affiliations and thus mental illness was
considered a punishment from God for wrongdoing or a warning to do better by higher
powers such as God and ancestral spirits.
Cultural Inferences of Mental Illness
Mental illness was viewed as “social misfits in society.” All 10 participants
mentioned fear of being shunned away from their communities or being seen as an
outcast if mental illness was revealed. P2 stated, “also I feared being cast out of the
African communities and become more isolated, so I just stayed quiet”. Mental illness
was also viewed as “curses from ancestral spirits” and thus needed sacrificial procedures
to overturn it. P8 stated, “cast out the demons as well as have traditional rituals to remove
the demons”. Others mentioned bad omens and familial spirits overtaking families. P9
stated, “mental illness is an omen. people do not talk about it. It is discriminated as a
man, it is shameful, and one is seen as weak for having a mental illness, so you suffer in
silence.” P10 stated, “maybe the great grandparents were not happy and sent the

disease”. There was a heavy reliance on traditional cultural practices in the perceptions of
mental illness as mentioned throughout by the participants. P6 mentioned, “in our culture,
you do not expose the crazies, you have to talk and please the ancestral spirits,”. When
asked what crazies meant, the participant stated, “mentally ill persons.” P4 also reported
traditional rituals reliance in response to treatment of mental illness, despite being a
Christian, he would have to perform the traditional activities with elders of the
community to ensure the mental illness was removed from his family “there are other
traditional rituals that can be done even with prayer”.
Causes of Mental Illness
In terms of what causes mental illness, there was an interrelation of both social
and cultural/religious ideologies. All ten participants mentioned that there was spiritual
causation of mental illness and three quoted Bible verses showing that mental illness was
spiritual. P3 stated, “we are a spirit, and we live in a body, so we have to deal with the
spiritual things spiritually before getting to the physical things.” Other respondents felt
that mental illnesses are caused by socio-economic hardships and environmental and
cultural changes from immigrating to the United States though they still tied the
economic hardships to religious aetiologies. P10 for example stated, “I had postpartum
depression and had a lot of financial hurdles, but God allows hardships to make us
stronger”. Interestingly, despite most of the participants having a bachelor’s degree and
earning more than $80,000 annually, the changes in their socioeconomic status were still
attributed to religious blessing rather than education. P3 stated “God has now blessed me
with better health insurance” while P5 mirrored the same sentiments “now that God has

given me riches and having insurance, I receive better care but without it, mediocre care
is given”. Some statements for causes of mental illness were “not being religious enough”
which on probing questions was clarified as “not praying enough and not attending
services enough.” All participants mentioned “lack of praying” as part of the causation of
mental illness. P1 mentioned she had severe anxiety from hormonal imbalance but stated
she had exhausted and addressed religious causes including more prayer and fasting
despite being ill before having laboratory findings to confirm hormonal imbalance. The
participant still attributed the diagnosis as a religious blessing due to the biological cause
rather than mental illness. “God answered my prayers and now I am healed but I still take
thyroid medications.” Regarding individual experiences with mental illnesses, eight
respondents stated they had not personally experienced mental illness but described
situations where “it could have been distressing.” One participant stated, “maybe it was a
mental illness like depression, but I wouldn’t call it that because I do not want to label it.”
Others report divorce, domestic violence, work-related stressors, and loss of loved ones
could result in a period of “feeling down” but should not be called depression as the
terminology is a western term. P10 stated, “Even those who encourage you to get help tell
you to speak in faith and not mention your symptoms or diagnosis so as not to make it
come to you. It’s an isolating season”.
Theme 2: Treatment of Mental Illness
The second theme was the treatment of mental illness. The theme emerged from
questions regarding how the participants thought mental illness should be treated, views
of psychiatric medications, treatment for their children as well as experiences in hospitals

and clinics. This theme answers the research questions regarding the experiences of
African immigrants in the United States with mental health care as well as how religion
influences mental health care use among African immigrants in the United States. The
categories under this theme include cultural influence, religious influence, formal mental
health care perceptions, experiences with the mental health care system, and
stigma/shame associated with disclosing mental illness.
Cultural influence
All ten respondents mentioned that in their countries of origin, they relied on
cultural measures in the treatment of mental illness. The measures mentioned are “talking
to elders, seeking ancestral powers to please them,” using traditional African healers as
well as consuming “certain foods known to heal mental illness.” Some of the traditional
practices mentioned were offering “blood from goats to the ancestors” which was
mentioned by five of the participants while others mentioned traditional practices but did
not feel comfortable elaborating or explaining the practices. Despite their western
religious affiliations, there was an interrelation of the African traditional religious
systems such as worship of ancestral spirits which were intermingled with the cultural
perspectives thus difficult to delineate between the two. All the participants despite their
religious faiths mentioned cultural/traditional measures as done in their countries of
origin. P5 stated, “we use the blood of goats in our culture to appease the ancestors”
while P4 stated, “I do not do those rituals anymore, but my family will still do it for me, I
would rather pray”.
Cultural traditions are also noted to dissuade seeking formal mental health care.

P8 stated when responding to treatment of mental illness, “Isn’t that American thing?
people stay in America too long and start behaving like them, …. if I did, some people
from my culture would alienate me and find me too westernized…,” while P9 stated in
responding to seeking formal mental health care “that is not how we do it as Africans”. A
post-graduate participant P10 stated, “despite being in the medical field, I never thought I
could get depression as an African, we are strong, these are American diseases. But now I
have changed my mind about getting it”. There was also a gender variation in mental
illness treatment, as male participants mentioned their perceptions of how an African man
should behave. “I am an African man, I tough it out and not cry about it” and “I am
expected to be tough, hard, and emotionless.” P5 stated “I just manned up and toughed it
out. I did not seek help. It was a functional depression where you are still in public but
suffering in silence”
Religious Influence
Religious practices were highly relied upon by all participants and were their first
preference in dealing with mental illness. Religious practices were mentioned by all ten
participants with statements like “more prayer and fasting” and “talking to spiritual
leaders” being the common reoccurring theme. P1 stated “mental illness isn’t real, it's
maybe demonic thing going on, and they feel like you can also just pray your way out” in
response to how African immigrants viewed mental illness referring to the generalized
community understanding of mental illness. P3 stated, “If you are mentally ill, they think
you are demon-possessed. Something has come on you and you need demons to be cast
out or you need prayer.” All participants mentioned that mental illness had spiritual

inferences to it and thus they had to consult religious measures for healing. Half of the
participants mentioned that “medicines cannot even work without praying first.” P5
stated “you have to engage both together. I think they work interdependently with each
other. Religion can help mental wellness when they are both used together with medicine,
if not, then it makes it less impactful and hinder mental wellness. Religion offers hope
and a good expectation, so I think it fosters mental wellness especially when it is used in
conjunction with mental health care.” P3 mirrored the same perceptions by stating
“honestly, I would start with spiritual first then do medical. But that is not only mental
health, it is all medical issues. God is in charge; I would not take medicine without prayer
first. So, I will pray the sickness away first even with a tummy ache or headache.” The
participants inferred that prayer and fasting provided “hope” which in turn created a
healthier environment where medical interventions would be successful. On experiences
with mental illness, all stated a spiritual connotation of each experience such as “I would
pray for them more,” “I would fast more,” and “I felt better after praying and singing
worship songs.” There was no difference in opinion between Protestants,
Nondenominational or Catholic participants in terms of religious influence in the
treatment of mental illness. Non-denominational participants did discuss being open to
collaboration between both medical and spiritual treatments whereas Protestants and
Catholic participants mainly relied on prayer.
Formal Mental Health Care Perceptions
Formal mental health care was not highly regarded among participants. Eight
respondents indicated that they would not seek psychiatric help as a first option if they

had a mental illness. Those who were against seeking psychiatric support feared stigma
and discrimination, being looked at as people who are cursed, social misfits, or possessed
by demons. They also indicated that seeking formal care for mental illness was not an
African thing to do. P2 stated, “so it is more of like a Western thing, more than an
African thing. So, in the African culture they do not accept it hence they pressure you not
to get any help and use traditional or religious things.” P3 stated “So I will pray the
sickness away first” while p8 stated “No, I would not seek help, I can talk about it, pray
about it. medicines also have a lot of side effects while p9 stated, “a man I am expected to
be strong. Also, my nephew had mental illness and had to live in an institution for several
months, it is shameful and looked down on, that is why it is hard for people to be open
about mental illness. He is good now though but still takes medications.” Two of the
participants who stated they would seek help from a psychologist or therapist had
previous first-hand experiences with mental illness. In both cases, the participant sought
formal mental health treatment after exhausting all other options but reported relief
because of medical interventions. One of the two participants P2 stated “depression for
ten years and it got to the place where I could no longer work” before seeking health care
services. Similarly, P1 stated, “I had to go back to my home country, fast, pray and seek
ancestral help before accepting help from a psychiatrist…… I did not know psychiatric
help was an option for me.” The other eight participants stated they would only seek
medical care as last resort. Several statements such as “unless I could not get out of bed”
or “was walking outside on the streets naked” were noted.

In terms of the type of formal mental health care, all participants were more
comfortable with psychotherapy where they would say “therapy” or “talking” rather than
seeing a psychiatrist or taking medications. P10 stated, “I can go to therapy but not to
psychiatry or hospital. I feel that those areas are reserved for very sick people. It is also a
little embarrassing”. P6 who was against the terminology “psychotherapy” stated, “Tough
it out, maybe talk if necessary but do not call it psychotherapy, why do people get too
westernized? Anyway, avoid stressors. Go out and have fun and pray about it”.
There was an elevated reluctance in taking psychiatric medications among the
participants. Nine of the participants stated they would not take psychiatric medications.
Their reasons for the reluctance were fear of side effects, fear of addiction and inability to
function without the medications, and beliefs that the psychiatric medications were
different from regular medications and would permanently alter their mental functioning.
P5 stated, “medications change the way one thinks” while P1 stated, “so the doctors
prescribe me a bunch of stuff, and I never did take that. I was afraid maybe I would go
crazy; you know, I do not trust doctors because they only patch you up.” P6 stated that
“medicines only treat symptoms but not the cause of the illness” in response to reasons
for not taking psychiatric medications if needed. Follow-up questions on whether
participants would seek medical assistance with a physical illness all showed that all
participants would readily seek medical care with or without prayer for other illnesses but
not for mental illness. Psychiatric medication was also not perceived as “regular
medicine”. P5 stated, “those drugs are a hit and miss, they do not specifically target the
issue” while P9 stated, “the side effects are worse than the disease itself, medications for

mental illness are not in the same category as other medications”, P3 stated, “I can only
take the drugs for a very short time and wean myself off. I am a nurse; I know what those
medications can do”. P4 believed the medications would make mental illness worse, “I
think medication makes things worse, and what I’ll really try first is a certain diet to see if
you can help”. Upon probing which diet was suitable for mental illness, P4 reported it
was traditional green vegetables and fruits. There was also a fear that treatment could be
against God’s will. P9 stated, “what if the hallucinations were God talking to you and
then you take medications? It’s good to pray first”.
When asked about seeking mental health treatment for their children, there were
mixed feelings with a lot of hesitation in answering the questions. P10 stated, “that is a
difficult question because what would cause children to have mental illness apart from
the devil?” Six respondents paused before answering this question during the interviews
and appeared uneasy. The six would not seek mental health help if their children had a
mental illness to avoid discrimination, and fear of stigma on their children as well as their
cultural/religious beliefs. The hindrances were thus the same as those for adults in
seeking mental health care. P3 stated “I would protect my children at all costs, anything
that would make them be treated differently; I would not expose it at all” while P5 stated,
“speaking to a therapist would be okay but not medications, children are too delicate”.
Those who would not seek treatment reported they would wait it out before seeking help
and would rather pray instead. Of note, the two participants who had previous
experiences with mental illness and had sought help were willing to seek help if needed
for their children. They both had graduate level education and earned above $80,000.

Experiences with the Mental Health Care System
Regarding the question about the experience of immigrants in the US clinics and
hospitals compared to Africa, all respondents indicated that they faced racism or some
sort of discrimination while attending US clinics and hospitals. Two participants who had
sought mental health care, stated their experiences were negative. One stated the staff
would not believe her and thought she was pretending until she revealed her profession as
a medical professional. P2 reported “Once I told them who I was, then they believed my
symptoms and started treating me with respect. I had to come in with my scrubs for them
to treat me differently.” All the participants mentioned “accents” being part of the
problem in discrimination regarding accessing any kind of health care services. P2 stated
“as soon as you speak, they will treat you like you do not know what you are talking
about, as if Africans are not educated” P1 stated, “They treated me like an outcast due to
my accent and did not believe me”. P5 stated that he was regarded as an African
American until he spoke and things “quickly went from bad to worse”. P8 and P9
reported they avoided hospitals due to perceived bad treatment which they attributed to
their African descent as well as racism due to their skin color. P9 in response to treatment
at healthcare centers, stated, “they think we are primitive and speak down to us especially
when we do not have money. I think money and insurance would change how they treat
you”. P10 stated, “they start asking where I was from and asking if I see lions outside my
home, they believe everything in the media and treat us different”.
Participants also felt the American system was rushed and prescriptions were
given too hurriedly. P1 reported, “I was not being believed and was being quickly

prescribed medications without a thorough workup to get rid of me”. P1 reported she did
not take the prescribed medications. P5 also reiterated similar sentiments by stating
“They just want to get rid of me waiting in a waiting room and give me a band-aid
medication, so I do not trust the health system”. Discrimination and stereotypes were also
described by P10 “they would not give me pain medication on the second day after
cesarean section. I felt they looked at me as a drug seeker, they would not have treated a
white person the same”. Participants also reported feeling like misfits between two
countries: the country of origin and the country of residence. P1 stated “In the US, they
do not expect mental illness from us, they think that we need traditional help, or we are
just angry. In Africa, they think we are crazy. You do get treated differently, but like in
my case, they did not take me seriously. I saw 5 different doctors before they took me
seriously”. P2 reported, “In Africa, you are insane. In America, you are discriminated
against. Where do you get help?”
All participants reported perceived improved care with time as socioeconomic
status rose as they had better insurance policies that gave them access to a higher quality
of health care. In terms of recommendations to enhance mental healthcare among African
immigrants, respondents indicated that undertaking the education of people in the
community and ending retrogressive culture would be important in enhancing the use of
mental healthcare. P6 stated, “we need more education, more teaching, more
collaboration, and financial help to foster and teach people in the churches all would help.
So, the more tools we have, the more resources are available to reach more people.” P3
mirrored the same sentiments:

“I think we need to give information when people have the knowledge and they
know what to do regarding where they are or how to handle this mental illness,
make them aware that there are resources out there to help you, and this is how
you can go about it, even if you want to do it anonymously, in case there are
people who are still dragging behind because change for many people comes in
different ways”.
Ending racism and discrimination while creating synergies and collaborations was also
reported to be equally important in supporting the uptake of mental healthcare among
African immigrants. P5 stated, “If we are treated equally and there was less racism, it
would be easier to seek care not just for mental illness but other things as well”.
Stigma and Shame
There was noted apprehension in sharing their mental health diagnosis or
treatment with religious leaders and family members. The concept of shame was
mentioned by all participants where mental illness was frowned upon thus by both the
religious sectors and communities. Shame and stigma were noted in both the diagnosis of
mental illness, a family member having it, accepting treatment for it, or even taking
psychiatric medications. P10 reported in terms of mental illness diagnosis, “It is also a
little embarrassing to have mental illness” while p2 stated about her diagnosis of mental
illness “I felt ashamed, scared and judged and I still do not discuss it with other African
uneducated people because they still judge me”. Social maladjustment and
institutionalization of mentally ill people in the countries of origin also contributed to the
shame and stigma of mental illness. P6 stated, “We do not have mental illness in Africa,

we do not talk about it and people with mental issues stay in an institution or live on the
streets which is shameful” The component of sharing was also looked down upon due to
fear of transference of the “demon possession” P5 stated “since not many people
understand mental health in Africa and they will outcast you so it’s better to keep it to
yourself and if you talk, it could come on the other person” when probed on what would
come to the other person, P5 replied “mental illness or demons”
Of those who would seek mental health care, they would not disclose it to
religious leaders especially those back in Africa. About seven stated they would disclose
to the nuclear family in the U. S. but not to the family living in Africa since those living
in Africa would not understand and are more likely to judge and discriminate against
them. P10 stated, “With family members, it would be really hard to share. They are still
in the notion that mental illness does not affect Africans and it is a western disease or a
disease of weaklings”. P6 reported it was not African to share such information “Maybe, I
am not sure. No, I would not share it. It is not African to share such news. You keep it
close to yourself to avoid judgment. Being sick in Africa is not viewed the same as
America”. P3 reported, “because of my profession, I am comfortable discussing it,
especially in American circles but not so much in African circles due to being seen as
weak and deficient”. P1 stated, “In America, there is more acceptance of mental illness
among whites, and they view it as a regular disease so it’s easier to share with them, we
Africans still do not accept it”.

Theme 3: The Role of Religion in Mental Health Care Use
The third theme is the role of religion in mental health care use. The theme
emerged from questions regarding how the participants thought religion could assist in
supporting its members in mental health care use and what recommendations they would
provide to facilitate African immigrants to utilize mental health care. The categories
under this theme include education, normalization of mental illness, and collaboration.
This theme answers the research question; How does religion influence mental health
care use among African immigrants in the United States.
Education
In terms of what role religion plays in the use of mental healthcare, all participants
felt that religion did not assist in mental health care use and could do more to augment
mental wellness among African immigrants. Participants indicated that religion and the
church could play a key role in education in areas such as supporting the rehabilitation of
individuals with mental health issues, creating awareness of causes, prevention, and
treatment of mental health illnesses, and could support the management of mental health
issues through the provision of psychiatric therapy. Education from the religious
perspective was for both members and the leadership. P10 passionately stated,
“Religion needs to educate its members to demystify mental illness and stop
telling people its demons and aliens. Teach them about it, about mental illness
symptoms. Educate the pastors. Pastors feel like they know everything, and they
do not. Also, educate people that pastors are not gods, and they should stop taking

their final word as the only word. Rely on both faith and medicine. Faith without
works is dead”
Like p10, p3 stated, “Leaders also need to be more informed so that they can teach the
members and offer more than just prayer. There is too much emphasis on only the pastors
and some pastors do not know about mental health and need education too”.
Most of the participants reported an increase in the last 2-3 years of more
awareness of mental health in the media providing some ideas about mental health. P3
stated, “This is also new. In the last 2 years, they have started talking about mental illness
in the media but not so much in the churches.” P5 stated, “I think information is key.
When we lack information, we would perish, we do not have a lot of information. Yeah, I
think that is where we need to start from knowledge and empowerment empowering our
immigrants.”
P8 stated she only learned about mental illness in the last two months, “I have only now
started to learn more about it, I need more information”. All participants purported that
mental health was not discussed as much as they feel it should be in religious settings
such as the churches and most of their information was from the media outlets P4 stated,
“the churches are getting more versed with mental health though not as much as it needs
to.”
Religion among African immigrants was also noted to be a multifaced factor
since, despite the modern religious affiliations, most participants had traditional religious
beliefs intermixed with cultural beliefs regarding their perspective of life, wholeness, and
mental health. P7 stated, “I still need to be part of my culture so I cannot abandon my

African traditions and adapt only western beliefs” when questioned on the role of their
traditional religious beliefs versus their modern religious affiliations, the participants
stated they both work together as their families in Africa still rely on traditional faith. P10
stated, “I do not believe in them anymore, but my parents do so they pray and also offer
sacrifices, education is needed even in Africa” while p4 stated, “but my family in Africa
do not accept mental illness, they think it is spiritual and that you have a demon and will
perform rituals to cast out the demons or to make ancestors happy, while I prefer to pray”.
As a result, mental well-being among African immigrants was noted as a multifaceted
issue that could not be addressed through brick-and-mortar buildings but also through
traditional faiths as well as modern medicine. All participants stated that religious
affiliations should provide more education to their congregants regarding mental health
through education of signs and symptoms to ensure people recognize mental
illness and seek treatment. P5 reported, “maybe pastors should have mental health as part
of seminary courses to make sure the preachers know about it since most preachers do not
have sufficient information so they cannot guide us”.
On the question of whether pressure from religion would influence mental health
use, all respondents stated if their spiritual leaders talked about mental health and there
was more acceptance, they would be more likely to embrace and seek mental health care.
P3 stated regarding seeking mental health care and disclosing it to the religious leaders
“Yes, I would share with them as well, but it depends on whether they openly discuss
mental health. if they do, then it is easy to talk to them if not then it is harder, and they
cannot give me counsel.” P6 stated, “if my pastor encouraged me to seek mental

healthcare, then I would do it, but they do not talk about it”, while P4 reported, “If there
was less stigma in the church and mental illness was accepted, I would be more
comfortable seeking help”.
Collaboration
On the question regarding the role of religion in mental health care use, all ten
participants mentioned the need for collaborative efforts between health care and religion
to foster mental health care use. P3, P5, and P10 mentioned the phrase “Jesus and
therapy” which upon probing referred to collaborative efforts between therapists to the
church and making mental health counseling a part of religious activities. P3 stated,
“creating avenues for members to seek mental health, counselors, integrate care ministries
in the church like Sunday school classes so we can normalize mental health”.
P7 reiterated that “psychiatrists, therapists, and religious leaders should all come together
and learn from each other to make it a better place.” Collaboration was also used to mean
financial support to the religious organizations to improve the outreach and awareness
programs. P6 stated’ “more collaboration, financial help to foster and teach people in the
churches all would help. So, the more tools we have, the more resources we offer, the
better”.
All participants voiced that religion was preventing mental health care use among
the African immigrants. P2 stated, “In Catholicism, there is no space for that…. I feel that
it is never addressed, and no help is available for those needing help. The bishop and
priests should talk about it, and they should stop blaming people or calling them weak for
being mentally ill. It would really help,” while p1 stated:

“religion stigmatized people and prevents people from seeking help and I feel like
a lot of people have actually lost their lives, too, because they cannot talk, because
if you speak out, some like I said will say something is wrong with you, some
demons, or not praying enough, you're not close to God enough and it shouldn't
be happening to you, and they have all kind of scripture to back it up. So, the
church should take charge and start raising people, to understand that these things
are real, and people do need help. Both psychologists and medicine can help.”
Participants also voiced that seeking formal mental health care would not be fully
adequate without religious activities such as prayer. P1 stated, “so both faith and
medicine because God comes first use both collaborations absolutely for that education to
occur” while P2 stated, “we need to be talking about it because talking can increase
education in the churches. Education is looked upon in Africa and is very highly
respected so if that individual or those individuals start creating awareness by talking
about it there will be more awareness and collaboration with the church and mental
health.” P1 stated that “as much as I can take medication for mental illness, my faith
comes first, so there needs to be collaboration for both mental health and the church”. P5
stated “You have to engage both together. I think they work interdependently with each
other. Religion can help mental wellness when they are both used together, if not then it
makes it less impactful and hinders mental health, Religion offers hope and a good
expectation, so I think it fosters mental wellness especially when it is used in conjunction
with mental health care.” P10 also had similar thoughts and stated, “Rely on both faith
and medicine. Faith without works is dead”.

Normalization
All 10 participants mentioned that mental health should be talked about more to
reduce the stigma and discrimination in their communities when dealing with mental
health. Statements such as p5 stating “they would call me a lunatic if I disclosed my
mental illness” or “mentally ill people are institutionalized in Africa hence we have to
hide it” reflect the participants feeling that they need to hide mental illness to avoid the
shame associated with it. Hearing statements such as “you are not close enough to God if
you suffer from depression” as reported by P8 also reflect the participants’ feeling that
they were not part of the religious community due to their suffering from mental health
issues. P10 stated the same regarding depression as “a disease of weaklings” thus
isolating the sick individual from the very support needed at that time. P10 thus stated
“why can’t we just talk about depression and anxiety in the church, it exists but it’s all
hush hush” with p8 reiterating similar perceptions, “the church feels like they own your
whole entity, you cannot even feel depressed because then you are weak”. All participants
vocalized that “talking about mental health more” would help not only educate but reduce
the stigma associated with mental illness. P3 stated, “we need to make it normal like any
other disease so that it is more acceptable” P5 stated that since their religious leader had
discussed mental illness, he was much more accepting of it as a disease. The concept of
mental illness not being a real disease among African Immigrants in religious settings
also emerged. One participant stated, “nobody views this as a real disease”, another stated
“it’s not like a stroke or a headache”, and still another stated, “Jesus cursed demons from
that child, it’s not as real as they say”. Mental illness is thus labeled as an anomaly in the

religious settings with far in-between cases known making it a secretive disease to deal
with.
Evidence of Trustworthiness
As described in chapter 3, I set out to ensure that there was dependability,
credibility, confirmability, and transferability to enhance trustworthiness in the study.
Burkholder et al. (2016) state that a researcher’s commitment to the above factors can
ensure trustworthiness in research.
Credibility
Credibility ensures that the study is transparent and believable, and that the data
collected informs the study (Lueng, 2015). To ensure credibility in the study, I used
member checking and triangulation. Member checking was done by providing transcripts
from the audio recording to the participants to ensure that their experiences were fully
captured as they intended. All participants returned the transcripts and validated their
portrayal of their perceptions. Triangulation in data collection was also utilized in
ensuring multiple approaches to answering the research questions such as audiotaping,
journal notes, and observation.
Transferability
Transferability is the extent to which the study can be generalized (Burkholder et
al. (2016). Despite the sample size being small at ten participants, I provided a detailed
in-depth description of the demographics, the number of participants, duration of the
interviews, and data collection period which enables readers to identify the limitations of
the study that would affect transferability (FitzPatrick, 2019) The participant pool was

also varied from different parts of Africa; West, East, and South which provided a
variation in the study sample with varying experiences and backgrounds ensuring a rich
comparison of data and thus increasing transferability.
Dependability
Dependability is a component of trustworthiness that ensure that data stays
unchanging over time thus ensuring consistency (Elo et al., 2015). Triangulation in data
collection through audiotaping, journal notes, and observation provided consistency in the
data collected. Coding of the data both manually and through Dedoose also ensured the
consistency of the analysis. Digital audio recordings also keep the data available over
time and were stored on a personal password-protected computer.
Confirmability
Confirmability ensures that researchers can verify the study and have confidence
in qualitative research based on data rather than the researcher’s opinions (Ravitch &
Carl, 2016). Confirmability was maintained in the study by maintaining a reflexivity
journal to record my own opinions, and biases throughout the process to ensure I
remained objective.
Summary
This chapter described the data collection process and study sample, presented the
results of the thematic analysis, and provided evidence of trustworthiness. After
recruiting the participants via purposive sampling, I then conducted 10 interviews. All
interviews were audio recorded and transcribed. I reviewed transcripts for errors and did
member checking to ensure accuracy as well as to ensure the data answered the two

research questions. After coding, I developed three themes with 12 categories which
assisted in understanding the role of religion in mental health care use among African
immigrants in the United States. All participants had a vague understanding of what
mental illness was and reported the knowledge had been enhanced in the last few years
due to heavy portrayal of mental health in the media but had varied causes of mental
illness. There was a heavy reliance on religiosity on the causes of mental illness such as
demon possession, prayerlessness, sin et cetera. Treatment of mental illness was also
religiously based on prayer, song as well as African traditions such as pleasing ordinances
to ancestors. Psychiatric medication was highly frowned on as well seeking mental
healthcare unless as a last resort with combined religious activities. In the role of religion
in mental health care use, religion was found to be lacking in fostering mental health care
use though participants stated there needed to be more collaborative efforts from the
religious leaders as well as medical professionals in making mental health care more
easily accessible. Racism, as well as indifference in the health care setting, arose
especially when the participants spoke out and their “accents” were noted. The treatment
was noted to improve with increased socioeconomic status. More education to create
more mental health normalcy would likely reduce the stigma and shame associated with
mental illness as well as collaboration was a common recommendation provided by the
participants in the study. Chapter 5 will provide a discussion of the connection between
the literature categories and themes derived from chapter 4. Chapter 5 will also provide
an interpretation of the results, implications for practice, and limitations of the findings as
well as provide recommendations for future research.

Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of this ethnographic qualitative study was to provide an explorative
understanding of how religion influences mental health care use among African
immigrants in the United States. Ten individuals living in the United States, from various
African countries participated in semistructured interviews where they shared their
experiences with the mental health care system in the United States and discussed how
religion influences mental health care use. Five interviews were done via Zoom while the
other five done in person. There were no major differences between the interviews, but I
noticed the in-person interviews lasted longer and participants were more eager to have a
more conversational discussion compared to the Zoom interviews. This could be likely
from feeling more comfortable in person than through the Zoom platform. I used thematic
analysis to search for similarities and differences within the data which was used to
answer the research questions. I then chose commonly reoccurring ideas and summarized
them in a few words as my codes. The codes were then grouped into categories based on
their commonalities and then I grouped and organized the categories into three themes
that answer the research questions and were framed by TPB. Three themes and twelve
categories emerged to answer the research questions and to fill the gap in the literature on
how religion influences mental health care use among African immigrants in the United
States.
The key findings of the study were in the three themes: insight into mental illness,
treatment of mental illness, and the role of religion. There was a heavy reliance on
religion in both the interpretation of mental illness and the treatment of a mental illness

which provided a hindrance to mental healthcare use. Religion was not just the brick-
andmortar affiliation but also traditional practices which impacted the perception of the
participants regarding the diagnosis of mental illness and treatment. All participants
reported that they felt, at the current time, that religion was hindering mental health care
use due to a lack of normalization of mental illness in their respective denominations as
well as in their African communities. The ongoing media education on mental health
awareness was providing some education but there would be more acceptance if their
churches accepted mental illness. The religious leaders were also found to be very
influential on decisions about seeking mental health care. This chapter will provide an
interpretation of the findings, limitations of the study, recommendations, implications,
and finally, provide a conclusion for the study.
Interpretation of The Findings
This section describes how the findings from the study confirm, disconfirm, or
extended the current knowledge as noted in Chapter 2 of the literature review. The
section will also provide an interpretation of the study and analysis according to the
theory of planned behavior. Three themes were identified in the analysis with their
subsequent categories are outlined in Figure 3.
Figure 3
Organization of Themes and Categories
1.T :Insight on
illness
1.T :Treatment of
illness
1.T :Role of religion
Mental illness
• Categories • Categories • Categories
• 1. Causes of mental • 1.Cultural healing • 1.Education
illness practices • 2.Collaboration
• 2.Definitions of mental • 2.Religious healing • 3.Normalization illness practices
• 3.Cultural inferences • 3.Stigma and shame of mental illness • 4.Formal mental
• 4.Religious inferences health perceptions.
of mental illness • 5.Experiences with
mental health care
system
In Chapter 2, the literature review, the themes noted were religion, mental health
perceptions, acculturation, mental health care use, and stigma. The results of my study
confirmed similar themes/categories as shown above with insight into mental illness,
treatment of mental illness, and the role of religion as the overarching themes that
emerged from the study. The findings of this study provided meaningful connections
identified by the participant’s experiences regarding how religion impacts mental health
and mental health care use in the United States. Data from the literature review in Chapter
2 showed that religion played a role in mental health care use but did not elaborate or
define what role it plays. MHA (2020) stated that about 90% of the Black population in
the United States reported that religion influences their health and wellness. My study
confirmed findings to be accurate even among African immigrants. The results of my
study also described how religion influences mental health care use thus extending
previous research.
In this ethnographic study, the cultural views of 10 African immigrant participants
were explored to better understand their experiences as it pertains to the role of religion in

mental health care use. The study was designed to answer the following research
questions:
RQ1: What are the experiences of African immigrants in the United States with
mental health care use?
RQ2: How does religion influence mental health care use among African immigrants
in the United States?
I used TBP in this current study to understand mental health care use among African
immigrants in the United States as it pertains to the role religion plays in health
behaviors. I will thus discuss the emerging themes with corresponding research questions
to further interpret the results of the study.
Theme 1: Insight on Mental Illness
This theme answered the research question of how religion influences mental
health care use among African immigrants in the United States. Religion is found to
influence the insight on mental health among African immigrants in the United States.
The first theme is insight on mental illness which has four categories: causes of mental
illness, definitions of mental illness, cultural inferences, and religious inferences on the
insight of mental illness. The theme covered how participants viewed mental health as
African immigrants in the United States, how they thought it should be treated, and what
caused mental illness. This theme also covered any experiences participants had
previously had with mental illness to determine the extent of the knowledge they had in
recognizing mental illness.

All participants answered the questions describing what they believed mental
illness was and the consensus was that mental illness was any illness involving the brain
and thinking capacity. P2 stated “I think it is anything that affects how one thinks or
emotions, diseases of the mind.” P3 described mental illness as diseases that affect mental
status., P5 stated,
To me like the word suggests it means it is something that affects your mental
well-being, your psychological world, maybe which means the state of your mind
is how you think how you socialize and how you act, it's actually a state that
affects your emotional health. when I think of mental illness, I think of people
walking in the streets naked and do not make sense.
All participants mentioned their developing knowledge surrounding mental health due in
the past 2-3 years due to more publicity in the media regarding mental illness as well as
several participants’ own experiences with mental illness thus being more cognizant of
mental illness. One participant stated, “I never thought I could get depression as an
African, we are strong, these are American diseases. But now I have changed my mind
about it.” Other participants mentioned, “I have only learned about mental illness in the
last 3 years”, and “discussions about mental health are now happening but were not as
public before”. Mental illness definition thus changed as there was more exposure and
education in the media as well as firsthand experiences with the disease. The findings
thus confirm observations in Chapter 2 that discussed mental illness as understudied
among African immigrants and was not considered an actual disease but rather a “silent
crisis” (see Ojikutu et al., 2018). It also extended the current knowledge in showing that

with the current increase in mental health awareness in the media, more people were
becoming aware and developing some knowledge of mental wellness.
All participants also answered the questions regarding the cause of mental illness
where there were varied answers. The responses regarding the causes of mental illness
discovered were also consistent with the literature review of previous studies but with the
more added knowledge of how unresolved trauma and stressors can lead to mental illness.
Participants reported stressors such as divorce, financial hurdles, illness, and death as
contributing factors to mental illness. The stressors and trauma were however attributed
to influence from higher powers such as God and ancestral spirits showing the influence
religion had in their interpretation of life events. One participant attributed both mental
illness and economic hardship to the will of God, “I had postpartum depression and had a
lot of financial hurdles, but God allows hardships to make us stronger”, still another
participant stated in response to the causes of mental illness, “weak Christians who do not
pray or fast enough get mentally ill”. The overwhelming cause was thus from the
religious and cultural perspectives such as demons, evil spirits, and ancestral powers
which were mentioned by all participants, consistent with Chapter 2 literature review
showing that human inadequacies, spells, curses, and demonic spirits were attributed as
the causes of mental illnesses among African immigrants (see Agbemenu, 2016;
Habecker, 2017; Ludwig & Reed, 2016). Agbemenu (2016), for example, reported that
mental illness was described to be a result of human inadequacies such as wrongdoing
while Habecker (2017) noted beliefs of familial curses as some of the cause of mental
illness.

To assess their knowledge of mental health, I asked each participant about their
individual experiences with mental illness where most stated they had not experienced
mental illness but had seen persons in their African countries institutionalized with
mental illness or walking on the streets. The view of mental illness was thus of severe
cases of abandoned persons on the streets and institutionalized individuals. The
overwhelming sense was that a mentally ill person could not live a normal life in society.
One participant stated, “my nephew had mental illness and had to live in an institution for
several months, it’s shameful” while another reporting “We do not have mental illness in
Africa, we do not talk about it and people with mental issues stay in an institution or live
on the streets which are shameful” showing the connotation mental illness with the
severity of disease thus institutionalization or living on the streets. The views are
consistent with the knowledge gained from prior literature in Chapter 2 where mental
illness is viewed as an institutionalized disease or hidden to avoid shame.
Habecker (2017) reported that immigrants are less likely to abandon their
religious and cultural beliefs and thus their former years in their countries of origin
influence their views and perceptions in their new countries. This would explain the view
of mental illness as institutionalization or not an “African disease” despite being in a
different environment. There was difficulty noted in acceptance of mental illness
diagnosis among those diagnosed. Statements such as, “maybe I felt low, but I would not
use the word depression, that is too strong a word” while the other one said, “I never
thought I could get depression as an African, we are strong, these are American diseases.”
The participants who had experienced mental illness reported denial in accepting the

diagnosis or treatment for a long time. One stated, “I had depression for 10 years and it
was until I could no longer function that I accepted treatment”. The aspect and difficulty
of accepting the diagnosis as well as only viewing it from a perspective of severity thus
institutionalization add knowledge to current literature.
However, as the literature review revealed, the more enculturated the individuals
become, the better their health outcomes become in their new country according to Shoup
et al. (2020). My study results showed that with time the immigrants acknowledged
mental illness and accepted formal help without institutionalization. The participants also
expressed more acceptance of mental illness in America and thus they were more inclined
to share their experiences with nonimmigrant Americans rather than with their African
families as they did not receive rejection or shame. P6 stated “because of my profession, I
am comfortable discussing it, especially in American circles but not so much in African
circles due to being seen as weak and deficient”. This is consistent with an appraisal of
beliefs in the theory of planned behavior where if the appraisal is positive (no judgment
or shame), then behavior engagement is more likely (seeking mental health care).
This theme is consistent with the TPB which posits that attitudes toward a
behavior include their behavioral beliefs (see Asare, 2015). Behavioral beliefs are the
concepts and ideologies that a person has that inform and guide their decision-making
capabilities (Asare, 2015). The perception or insight on mental illness is the beliefs they
hold about what mental illness is, how it is recognized, and how it should be treated.
Erroneous beliefs lead to erroneous behavioral intentions and thus inform decisions
(Vaismoradi et al., 2016). In this case, when mental illness is identified as caused by evil

spirits, curses, weak Christian living, or offending ancestral spirits, the treatment will be
geared towards overcoming the aforementioned factors rather than seeking medical care.
Consequently, formal medical care is of limited use in such a belief system since religion,
whether religious affiliations or traditional religious activities, govern their care. The
theme is reinforced by previous research as well noting that the behavioral beliefs among
African immigrants would need to be addressed from the religious perspective which they
heavily rely on before formal mental health education (see Adu-Boahene et al.,
2017; Echeverria-Estrada & Batalova, 2019; Ekwonye et al., 2021).
Theme 2: Treatment of Mental Illness
The second theme was the treatment of a mental illness which arose from the
questions about feelings about seeking mental health care, how mental illness should be
treated, whether the participants would seek mental health care for themselves or their
families, and views on taking psychiatric medications or seeing psychiatrists. Religion
again was found to influence the views on the treatment of mental illness based on their
interpretation of mental illness from a religious perspective. The experiences with the
mental health system in the United States are also explored in this section to understand
their lived experiences with the healthcare system. This theme answers the research
question regarding the experiences of African immigrants in the United States with
mental health care use.
Regarding feelings about seeking mental health care, there was elevated negative
connotation in seeking health care where participants preferred religious activities such as
prayer and fasting rather than medical care. Traditional rituals were also mentioned

several times as a remedy to combat mental illness. Traditional rituals and religion went
hand in hand without differentiation between the two indicating that African immigrants,
despite having modern religious affiliations, still considered traditional rituals as part of
their religion. Religion was noted to be a major support in coping with mental illness
even among those who would consult formal mental health services. The participants
believed that religion augmented formal medical care and thus undertaking medical care
without religious support would yield ineffective results. These observations confirmed
previous studies that noted that African immigrants heavily rely on religion for overall
wellness, support, coping, and focus on life (see Adekeye et al., 2014; Olokotun et al.,
2019; Omenka et al., 2020). Seeking mental health care was also viewed as weak and a
Western behavior that Africans should not embrace, a concept noted in this study that
extended current knowledge on the subject. Those that would seek mental health care for
themselves, or their children stated they would not share the information with their
African families due to fear of stigmatization, shame, being shunned in their communities
as well as discrimination in their personal and religious circles. The findings mirror those
of Olokotun et al. (2019) who noted that even among educated parents who would seek
mental health care for their children, they were less likely to disclose such information to
African immigrants’ communities from the perceived shame of having a mentally ill child
as well as isolation from their communities that were their support system.
Stigma and shame were also noted in correlation to seeking formal mental health
services. Consistent with Nantwi et al. (2017), mental illness was to be dealt with in
silence and alone until it was gone. The word “isolation” was used by more than half of

the participants in describing how to deal with a mental illness meaning that one was to
keep it private and suffer in silence without involving the community. Stigma and shame
would resort to loss of community support and the value of community support among
African immigrants cannot be understated. The participants voiced their silence and
decisions not to seek mental health care if needed to avoid being shunned away from their
communities. As discovered in Chapter 2, their religious circles provided support and
were their focus of life (Omenka et al., 2020). Having community support is an important
aspect of the theory of planned behavior subjective norms. The study provided more
insight into the facilitation and interaction of social support and their decisionmaking
capacities. The participants would choose to have social interaction which was perceived
as support rather than share a mental illness diagnosis that would result in shunning from
the communities thus a perceived lack of social support. Their decisionmaking capacities
were thus influenced by the perceived behavioral control which is the ease of difficulty
associated with performing a certain behavior according to the TPB. Their religious
beliefs thus show that religion plays a role in delaying and impeding mental health care
use.
There was also a lack of knowledge in the religious circles as it relates to mental
health and its treatment. All participants stated they did not hear of mental health in their
religious institutions and only gained knowledge in mainstream media in the last few
years. Interestingly, almost all participants mentioned that if their religious leaders would
mention and talk about mental health, they would be conversant in sharing and accepting
mental health services. One of the participants mentioned that they were more accepting

of mental illness since their leader had discussed it in church but would not have
otherwise accepted it. The findings in the current study are consistent with Agyekum and
Newbold (2016) and Nantwi et al. (2017) where the role of religious leaders was explored
as an essential element with African immigrants in health-seeking behaviors and those
religious leaders had a paramount influence on the decision-making of the congregation.
The study thus provides insight into how religious leaders may use their influence to
increase mental health care use.
Regarding experiences with the health care system, this study confirmed previous
findings of lack of use of mental health services until the disease was severe. Ludwig and
Reed (2016) also noted perceived overdiagnosis as an issue which was confirmed in this
study. Also, this study expanded on a different concept where medications were
prescribed without much testing to “get rid of the patient” thus extending current
knowledge. The participants felt “ignored” and “not understood” by healthcare providers
resulting in visiting multiple doctors or stating their professional qualifications to get the
necessary assistance. The views of misunderstanding are consistent with NAMI (2021)
where cultural competence in health care systems was low with the incomprehension of
accents and lack of cultural awareness of African immigrants. NAMI (2021) reports that
the black population is more likely to use physical symptoms to describe mental health
issues thus a provider unfamiliar with this phenomenon is likely to misdiagnose or
misunderstand the patients if they do not probe for further information. This phenomenon
was noted when participants preferred to say sadness rather than depression as well as the
perception that hallucinations were not necessarily a negative symptom as it could be

God speaking to them. Being aware of the description of these symptoms would
consequently be essential for providers to understand when treating African immigrants.
Racism and discrimination were also an issue in the healthcare system as well as
disparities in care where the type of medical insurance and location of the clinic dictated
the quality of treatment received by staff in the healthcare system. Accents were a major
focus in access to treatment where the immigrants felt ignored, stereotyped as primitive,
and treated differently due to their ethnicity and accents. The experiences are consistent
with the TPB where perceived behavioral control is the ease or difficulty in performing a
certain behavior. The experiences created difficulty in mental health care use which in
hand resulted in reduced mental health care use. Asare (2015) states that decreasing
barriers to care such as reduced racism, and reduced language barriers can thus increase
in the ease of performing a behavior. Reducing these barriers can therefore reduce the
increased difficulties and reluctance in mental health care use and would hopefully be
beneficial in easing the opportunities for seeking mental healthcare to willing individuals.
Fears of psychiatric medication was also noted which was a new theme not noted
in the literature review. Participants stated they were more comfortable if needed in
therapy though they preferred to call it “talking to someone” rather than using
“psychotherapy” which was a more medical term that would result in labeling and likely
referring to they needed help. Fear and hesitancy were also noted in medical diagnoses
where calling depression “feelings of feeling down” but not calling it depression was
preferred. Psychiatric medications were referred to as “different categories” “had more
side effects” addictive” and “worse than the disease itself.” This view was consistent

among all participants including those who had sought medical care for mental illness but
refused the medications or weaned themselves off after a few days due to fear of “side
effects” or “feeling worse”. Despite the fear of psychotropics not being noted in the
literature review, it could be related to the findings of Freeland et al. (2020) that African
immigrants felt western healthcare providers over diagnosed patients and thus prescribed
more medications compared to African countries. This hence led to hesitancy and
mistrust in taking prescribed medications.
Asare (2015) reports that attitudes towards behavior in the TPB influence every
aspect of the behavior and thus affect the outcomes. In this case, the attitude or fear was
likely due to the skewed view of mental illness, its causes, and treatment which
inadvertently created qualms of the medications. Statements like “what if God was
talking to me and I took medications” further strengthened the causation of mental illness
thus treatment could interfere with their religious views. Of interest, the medication
uncertainty did not extend to other medications where on probing questions, participants
would readily take other medications for other diseases but not for mental illness.
Changing the attitude towards mental illness causations could thus change the attitude
towards mental health care use which would include acceptance of the diagnosis and
treatment using various psychiatric mental health care plans.
Vaismoradi et al. (2016), report that social pressures or subjective norms in a
society influence performance of behavior where if the community supports the behavior,
there would be more acceptance of the behavior. When there is a higher acceptance of
medications in the African immigrant community, there would more likely be more

mental health care use and acceptance of treatment modalities prescribed. Increasing
acceptance could be a result of increased education in the community regarding the mode
of action of the medications thus demystifying the common ideologies regarding
psychotropics. Monnapola-Mazabane et al. (2021) reiterate that when the appraisal is
positive, engagement of the behavior would also be more likely.
Although an increased level of education is often correlated to increased health
care use, education did not seem to change or alter the perceptions of mental health care
use or causation in this study (Fan et al., 2020). All participants in the study supported
these perceptions regardless of education level. Their education level and subsequently
increased socioeconomic status as shown on demographic data regarding income levels
were also attributed to a religious blessing rather than a rise in the socio-economic ladder
from their educations and consequently better jobs. This reflection further supports the
efficacy of religion as the lens to every aspect of the African immigrant’s life including
wellness which is consistent with previous studies (see Ekwonye et al., 2021; MHA,
2020; Nantwi et al., 2017; Omenka et al., 2020; Saasa, 2019; Ting & Panchanadeswaran,
2016; Wharton et al., 2018).
Theme 3: The Role of Religion in Mental Health Care Use
The third theme was the role of religion in mental health use which included three
categories: education, collaboration, and normalization of mental illness. The theme arose
from questions regarding how religion should support mental health care use as well as
recommendations for African immigrants in dealing with mental illness. The role of
religion in mental health care use among the participants was in educating the members,

collaborating with other organizations to deliver care in religious settings, and reducing
stigma through the normalization of mental illness. This theme answered the research
question regarding the role of religion in mental health care use among African
immigrants in the United States. All participants indicated that more education was
needed regarding mental illness. Interestingly despite their education levels, they
reiterated that education was needed in their religious settings to demystify the current
notion of mental illness being a curse, inadequacy, being weak, being un-African et
cetera. The participants felt that if education came from the pulpit, then they were more
likely to not only accept mental illness as any other disease but also likely to engage in
mental health care usage. The findings augmented the literature review finding that
religious leaders’ panegyrization of mental health could influence their behavioral beliefs,
which in turn could increase the perceived behavioral control to perform the intended
behavior (Lefevor et al., 2020). The findings also expand on available literature that
despite higher levels of education among African immigrants, religious teaching had a
greater influence on mental health beliefs and behaviors.
The role of religion was identified currently in this study to be inhibiting mental
health care use through ignorance of mental illness as well as skewed perspectives.
However, despite knowing that there were medical causes of mental illness, there was a
noted need to include the religious causes of mental illness and report the need for
collaborative efforts between religion and mental health care organizations. The concept
of only medical care was seen as deficient by the participants but when collaborated with
spiritual care, it was synergistic towards wellness and wholeness. The realization of this

knowledge extends the current data on the need to have collaborative efforts between
religion and health for effective health education among African immigrants. TPB
discusses behavioral intention as the true extent of performing behaviors when resources
and skills needed are available (LaMorte, 2019). The collaboration of health care and
religion would increase behavioral intention and thus increase mental health care use.
Education was not only needed for African immigrants but also for the African immigrant
clergy who have a propensity to lead the African immigrant faith institutions
(Sackey-Ansah, 2021)
More than half of the participants discussed the need for their spiritual leaders to
be more versed in mental wellness. The leaders were thus seen as the main barrier as their
normalization of mental illness would not only reduce stigma and acceptance but also
increase the use of the services. The observations of the study in participants stating that
their religious leaders did not speak of mental health were consistent with Payne and
Hays (2016) study showing that religious leaders felt ill-equipped in handling mental
illness and thus did not discuss it or discussed it very seldom with one sermon a year
being an average. The lack of normalization through open discussion of mental health by
religious leaders potentially creates a barrier in mental health care use thus reducing
perceived behavioral control. Perceived behavioral control consequently dictates that
mental health/illness is a complicated issue to deal with among the congregation leading
to further isolation, shame, and stigma of mental illness. With the normalization of mental
illness, the ease of accessing or discussing mental health issues would increase. African
immigrants would hence be more likely to access and use mental health care services as

noted in this study where the participants voiced they would be more amenable to seeking
help if the religious leaders talked about it.
Normalization of mental illness was mentioned by all participants in discussing
how religion should support its members with mental illness. According to the theory of
planned behavior, removing barriers in performing a behavior is more likely to increase
the behavioral intention towards the behavior (LaMorte, 2019). In the normalization of
mental illness, associated stigma, discrimination, and feelings of being weak and
inadequate would be reduced thus increasing the ease of not only discussing mental
illness but also use of mental health care services. Having mental health discussions
within families and religious groups/institutions which are noted as the support system for
African immigrants (Ekwonye et al., 2021; Omenka et al., 2021) would thus promote
mental health care use. Previous research however showed that the more acculturated an
individual was, the more likely they were to adopt health-seeking behaviors (Habecker,
2017). Despite most of the participants being in the United States for at least two decades,
they still preserved their immigrant country’s perception of mental health with heavy
reliance on religion to interpret it for them. Ekwonye et al. (2021) noted that there was
also identity confusion between assimilation into American culture versus maintenance of
their African cultures where immigrants felt too “African” to be called African
Americans yet too “American” to be regarded as African. Habecker (2017) explained that
despite multiple years of immigration, some immigrants did not leave their cultural or
religious beliefs, especially among first-generation immigrants who composed all the
participants in this current study thus explaining the retention of immigrant country

perception of mental illness. The need for health care providers to be conversant with the
African culture and retention of cultural/religious beliefs among African immigrants is of
utmost importance despite the length of time spent in the immigrant country, to deliver
optimal health care.
Limitations of the Study
This study had some limitations. The sample size was small with a limited number
of participants. Despite 10 participants being adequate for the qualitative study with noted
data saturation, the sample remains too small to generalize the study findings to all
African immigrants in the United States thus reducing the transferability of the study
results to the general population. Purposive sampling also created a limitation since all
participants had to fit the inclusion criteria thus there was a lack of random sample to
create a more diverse outlook such as those who did not speak English or those who were
older who may have had varied experiences. The study would have also benefitted from
being broader to cover other locations and States thus giving more diversity and
generalization. An additional limitation was that the study did not have any north African
participants and thus may not reflect the experiences from immigrants from northern
Africa. As a result, interpretations cannot be generalized to North African immigrants that
may not only have different religions but may also have different experiences.
Another potential limitation was the length of time the immigrants had been within the
United States and how that impacted how religion influenced mental healthcare use since
the participants reported their outlook on mental illness had just recently changed in the
recent years despite most having been in the country for more than a decade.

Recommendations
The study can be used as a baseline for future research to launch more studies in
which the identified roles of religion can be utilized to increase mental health care use
among African immigrants. Future qualitative and quantitative research can also be done
with a larger sample including all geographic parts of Africa to gain more transferability
and generalization of the study results. Future research could also examine the role of
socioeconomic status on mental health care use among African immigrants since it is
associated with improved healthcare access (Fan et al., 2020). More studies on different
religious affiliation roles in influencing mental health care use to gain a deeper
understanding of how modernization on religion affects health care use.
In public health practice, having collaborative efforts between mental health
providers and African immigrant religious institutions would provide firsthand
information and cultural competency to providers, the clergy as well as the congregation
thus improving mental health among African immigrants in the United States. Cultural
competence among providers should also be improved and expanded for providers and
public health officials working with African immigrants to provide holistic centered care
to the population. In faith-based institutions, the normalization of mental health and
illness by the clergy can be encouraged by fostering conversations through having trained
faith-based therapists offering their services in the faith-based institutions thus creating a
synergy between religion and mental health. Adding educational requirements for
faithbased leaders within the African immigrant population on the topic of mental illness
can be also important to demystify mental illness thus making them more likely to not

only discuss mental wellness in the faith-based institutions but also making collaboration
with mental health care organizations more feasible. Inclusion of religiosity in African
immigrants’ treatment plans among providers is essential while gathering data as their
wellness is attributed to their religiosity.
Implications
This study has contributed to filling the gap in the literature regarding the role of
religion in mental health use among African immigrants. On the individual level, the
study implications have resulted in more mental health discussions with African
immigrants thus beginning the much-needed conversations about mental health among
study participants and their families which reduces barriers such as stigma associated
with mental illness (Omenka et al., 2020). On the organizational level, more information
is provided on African immigrant culture and religious views which creates cultural
awareness. Cultural awareness can lead to cultural understanding among the care
providers treating African immigrants thus creating a positive social change through
improved health outcomes among the African immigrants as well as the increased
perception among the providers. The study findings increase more data on African
immigrants in the United States that can be shared with health providers, clergy members,
mental health providers, teachers et cetera. Sharing of the data can expand cultural
knowledge on African immigrant health not only in health care but also in schools, and
faith-based institutions thus providing more awareness of the experiences of African
immigrants with mental health which contribute to a positive social change in rising
mental health education level. Wharton et al (2018) report that increased awareness of the

mental illness and stigma associated with mental illness demystifies the disease thus
increasing wellness among those who suffer from it. The information gained in this
research can also inform policymakers in mental health care as well as religious settings
about the need for collaborative efforts between religion and healthcare. Endeavors such
as inviting mental health providers to speak in churches or religious leaders to speak in
mental health clinics promote cooperation and increase knowledge hence creating a
positive social change for not only the providers and the clergy but also African
immigrants seeking mental health care from increased education. Gained knowledge in
this study also increases the database on African immigrant health and serves as a
continued unveiling platform for further qualitative and quantitative studies among
African immigrants in the United States.
Conclusion
I embarked on a study to understand the role of religion in mental health use
among African immigrants in the United States. This was an ethnographic qualitative
study that aimed and achieved to understand the experiences of African immigrants in the
United States health care systems as well as an understanding of how religion influenced
their mental health care use. NAMI (2021) reports that one in five adults suffers mental
illness every year in the United States and ADAA (2022) reports that the leading cause of
disability worldwide is mental health illness. With the African immigrant population
doubling every decade since 1970 (U.S. Census Bureau, 2020), Adu-Boahene (2017)
states that there is increased underutilization of mental health care among African
immigrants. There is a lack of mental health literacy among African immigrants as mental

illness is not discussed nor treated in African communities unless very severe (Omenka et
al., 2020). The results of this study suggest that mental illness is attributed to curses,
omens, evil spirit/demon possession, inadequacies in religious living et cetera with little
connection to the hormonal or physiological causes of mental illness. The study findings
identified religion as a barrier to mental health care use due to erroneous interpretation of
the perception of mental illness, its treatment, an overall lack of discussion of mental
health among religious leaders or members, increased stigma, and the increased
discrimination associated with mental illness in religious circles. Mental illness is thus
not accepted as a disease and is often ignored in religious settings with a focus on more
prayer, fasting, righteous living, or traditional rituals rather than formal treatment. The
study identified that religious institutions, as well as religious leaders, can play a role in
educating their members, collaborating with mental health organizations as well as
normalizing mental illness to create more awareness. The role of religion is thus
education, demystifying mental illness, and normalizing mental health care.
The study has implications for positive social change in increasing awareness,
cultural sensitivity, and education, as well as invoking discussions around mental health
among African immigrant communities. Each participant was not only eager to voice
their need for more education but also more acceptance of mental health when embraced
by religious leaders. This study was designed with the goal of providing empirical data
that can be used to inform continued mental health discussions with religious leaders and
mental health providers. Increased awareness and education on mental wellness would
improve the overall health and wellness of African immigrants in the United States which

can improve health care use. This study shows that it is thus critical to understand cultural
and religious views when seeking to address mental health needs among African
immigrants’ populations which would in turn improve the use of mental health services.

