


THE RELATIONSHIP BETWEEN CREATIVITY AND RESILIENCE IN MENTAL
HEALTH PROVIDERS FOLLOWING THE COVID-19 PUBLIC HEALTH
EMERGENCY
CHAPTER 1: INTRODUCTION
The purpose of this dissertation was to examine the predictive relationship between
creativity and resilience in mental health providers who experienced volatility, uncertainty,
complexity, and ambiguity (VUCA) while working in the United States during the COVID-19
federal public health emergency period of January 31, 2020, to May 11, 2023. The goal of this
study was to determine the relationship between creativity and resilience and identify relevant
factors that contribute to resiliency which can mitigate secondary traumatic stress symptoms in
mental health providers. This research is important to identify factors of resilience to combat
secondary traumatic stress and create a sustainable workforce.
My interest in this topic emerged from my work as a community mental health leader
during the COVID-19 pandemic, where I experienced the evolving needs of mental health care
providers responding to the crisis. During this time, leaders needed to respond to the ongoing,
cumulative impact of stress and find methods to build resiliency. The typical self-care strategies
to mitigate secondary traumatic stress were not enough, and I found myself and my staff
overwhelmed, exhausted, and burned out. As an artist and art therapist, I used painting and
drawing as daily practice to process the events of the day. I found this time healing and
clarifying, often leaving my creative practice with new ideas and perspectives to the problems of
the day. As a creative and innovative thinker, I wondered how creativity could be used to foster
resiliency for other leaders and mental health care providers impacted by the strains of the work,
as well as how creativity could serve as a protective factor in the prevention of secondary

traumatic stress. The response model could no longer be reactive but instead needed to adapt to
navigate the volatile, uncertain, complex, and ambiguous (VUCA) environments that we lived
and worked within to generate resiliency within self and the collective system. In adverse
environments such as these, creativity and innovation can be useful skills in problem-solving,
especially when new and complex issues arise (Mumford & Todd, 2019). Creativity can foster
flexibility, presence, problem-solving, and risk-taking (Arnout & Almoied, 2020; Cropley, 2020;
Reisman et al., 2016). As such, creativity can help cultivate adaptation to uncertainty and
ambiguity, potentially contributing to resiliency factors necessary in mitigating secondary
traumatic stress and burnout.
Chapter 1 includes an introduction to the research proposal topic. Subsections include a
description of the problem, the purpose statement, and the research questions that will guide the
research and hypotheses. Chapter 1 also includes a description of the research method and
design, theoretical framework, definitions, study feasibility, and the significance of the research.
This chapter concludes with a summary and introduction to Chapter 2, the literature review.
Statement of Problem
The COVID-19 pandemic revealed inadequacies in health care systems and the
emergence of chronic volatile, uncertain, complex, and ambiguous environments (VUCA)
(Halawi et al., 2020). U.S. health care providers were overwhelmed and operating without
predictable and collaborative resources, and issues of secondary traumatic stress, which existed
prior to the pandemic, were amplified, leading to burnout (Halawi et al., 2020; Sorenson et al.,
2016). Mental health issues drastically increased due to challenges of isolation, stress, and
economic strain, placing amplified burden on mental health providers who were simultaneously
navigating changes in delivery of care and their own pandemic-related stressors (Fish & Mittal,

2021). Responding to these changes required flexibility, adaptation, and problem-solving to
ameliorate burnout (Sklar et al., 2021). Mental health has traditionally not been a central mission
within the public health workforce, and due to current findings on the intersectionality of
emotional well-being and mortality, mental health providers have become critical in promoting
national health (Fish & Mittal, 2021). The need to identify characteristics and practices that build
resilience in providers is critical to create a healthy, effective, and sustainable work force that can
adequately address the growing health needs of our nation.
Purpose Statement
The purpose of the quantitative, predictive correlational study was to examine the
predictive relationship between creativity and resilience in 171 mental health providers who
experienced VUCA while working in the United States during the federal public health
emergency period of the COVID-19 pandemic, which began on January 31, 2020, and ended on
May 11, 2023 (Silk et al., 2023). Identifying creativity factors that contribute to resiliency might
mitigate secondary traumatic stress symptoms in mental health providers.
Research Questions and Hypotheses
R1: What is the predictive relationship between creativity and resilience in mental health
providers who experienced VUCA during the federal public health emergency period of the
COVID-19 pandemic?
H10: There is no predictive relationship between creativity and resilience.
H1a: There is a predictive relationship between creativity and resilience.
R2: What is the predictive relationship between task creativity and resilience in mental
health care providers who engaged in creative activities during the federal public health
emergency period of the COVID-19 pandemic?

H20: There is no predictive relationship between engaging in creative activities and
resilience.
H2a: There is a predictive relationship between engaging in creative activities and
resilience.
R3: What is the predictive relationship between professional quality of life and resilience
in mental health care providers who experienced VUCA during the federal public health
emergency period of the COVID-19 pandemic?
H30: There is no predictive relationship between professional quality of life and
resilience.
H3a: There is a predictive relationship between professional quality of life and resilience.
R4: To what extent does secondary traumatic stress moderate the relationship between
creativity and resilience in mental health care providers who experienced VUCA during the
federal public health emergency period of the COVID-19 pandemic?
H40: Secondary traumatic stress does not moderate the relationship between creativity
and resilience.
H4a: Secondary traumatic stress does moderate the relationship between creativity and
resilience.
A sufficient sample size was not obtained to conduct research question 5.
R5: Which factors of creativity predict resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic?
H50: No factors of creativity predict resilience.
H5a: One or more factors of creativity predict resilience.

R6: Which subfactors of creativity predict resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic?
H60: No subfactors of creativity predict resilience.
H6a: One or more subfactors of creativity predict resilience.
Research Method and Design
I used a quantitative method and a descriptive correlational design to examine the
research questions (Black, 1999). Through a predictive, exploratory correlational design, I
examined the association and predictive relationships through the administration of an online
survey of mental health providers in the United States. The quantitative correlational approach to
this study was appropriate, as findings from correlational research can provide understanding
into complex, real-world relationships, such as creativity and resilience following the COVID-19
pandemic, and assist researchers in developing theories and making predictions (Black, 1999;
Schumacker & Lomax, 2010). The purpose of this descriptive research was to provide a snapshot
in time of what mental health providers experienced during the COVID-19 federal emergency
period and their creativity and resilience in the immediate period following. The ability to
capture this moment in time is critical to the research questions, as they relate to mental health
care providers who worked during the federal public health emergency period of the COVID-19
pandemic.
A predictive relationship between creativity and resilience could provide insight into
developing models of care for mental health providers affected by secondary traumatic stress.
The population of mental health providers in the United States is a clearly defined, heterogenous
group, is a good fit for the research questions, and reduces population-specific bias (Daniel,

2012). A combined census and snowball sampling approach maximized response rate and
eliminate random sampling errors and selection bias (Black, 1999; Daniel, 2012).
The survey questionnaire consisted of demographics, Likert-type questions pertaining to
VUCA, professional quality of life, secondary traumatic stress, and task creativity, as well as the
instruments to measure creativity—the Reisman Diagnostic Creativity Assessment (RDCA;
Reisman et al., 2016)—and resilience—the Connor-Davidson Resilience Scale 25 (CD-RISC-25;
Connor & Davidson, 2003). Data analysis comprised of descriptive and inferential statistics,
including bivariate and multiple linear regression analyses to determine predictive relationships
between the variables (Black, 1999; O’Connel, 2006). Bivariate correlation was used to
determine the relationship between two variables and required a sample size of 95 (Field, 2018).
Theoretical Framework
The theoretical framework for this study was based on the theories of VUCA,
professional quality of life, resilience, and creativity. The term VUCA was coined in the 1980s
following the Cold War to describe the challenges related to geo-political volatility (Lehrner,
2021). Following its declaration by the World Health Organization (WHO) as a global pandemic,
COVID-19 gave rise to volatile, uncertain, complex, and ambiguous (VUCA) environments
(Dima et al., 2021; Murugan et al., 2020; Taskan et al., 2022; WHO, 2023). Unprecedented strain
was placed on health care systems, in particular mental health providers, who have traditionally
been marginalized from medical response efforts (Fish & Mittal, 2021). This study focused on
mental health care providers affected by VUCA environments caused by the COVID-19
pandemic and how they were affected by secondary traumatic stress (Figley, 2002; National
Child Traumatic Stress Network [NCTSN], n.d.-b). Secondary traumatic stress is defined as the

emotional duress experienced by providers in response to hearing another’s experience of trauma
(NCTSN, n.d.-
b). Literature was reviewed in the field of professional quality of life, which included theories of
compassion satisfaction, compassion fatigue, secondary traumatic stress, burnout, institutional
betrayal, moral injury, and related symptoms of cynicism, exhaustion, ineffectiveness, and
hopelessness (Brewer, 2021; Figley, 2002; Hopwood et al., 2017; Sklar et al., 2021; Sorenson et
al., 2016). Strategies to ameliorate the impact of stressors caused by VUCA were discussed in
relationship to resilience and creativity.
The capacity for resilience is described as the ability to adapt positively to quickly
changing environments and situations (Leask & Ruggunan, 2021). Resilience in the context of
provider health and well-being was discussed in terms of agility, self-care, polychronicity,
support, and creativity (Anser et al., 2022; Baskin & Bartlett, 2021; Leask & Ruggunan, 2021).
Resilience within VUCA environments relies on the capacity to adapt to foster stability through
vision, understanding, clarity, and agility (Dima et al., 2021). Creativity was introduced as a
mechanism for adaptation and agility to foster resilience during times of uncertainty, such as the
COVID-19 pandemic (Joiner, 2019; Wang et al., 2011; Worley & Jules, 2020; Zenasni et al.,
2008).
Definitions
VUCA is defined by its acronym representing volatility, uncertainty, complexity, and
ambiguity (Lehrner, 2021). This term relates to environments and has been used to describe
instability and the likelihood that circumstances can change quickly and significantly (Dziak,
2023; Lehrner, 2021).

Professional quality of life refers to the negative and positive effects of work-related
stressors on helpers (Stamm, 2010). The positive impact of professional quality of life refers to
the positive effects of work-related stressors on helpers, such as compassion satisfaction, sense of
purpose, increased productivity, mattering, contributing to the greater good in the lives of clients,
and fulfilling the human needs for self-efficacy, self-determination, and belonging. The negative
impact of professional quality of life refers to the negative effects of work-related stressors on
helpers, such as compassion fatigue, secondary traumatic stress, burnout, institutional betrayal,
and moral injury. Symptoms include fatigue, skepticism, and decreased personal and professional
efficacy. For the purposes of this study, the professional quality of life of mental health care
workers will be delineated using theories of compassion satisfaction, compassion fatigue,
secondary traumatic stress, burnout, institutional betrayal, and moral injury. Secondary
traumatic stress is defined as “the emotional duress that results when an individual hears about
the firsthand trauma experiences of another” (NCTSN, n.d.-b, para. 1). Symptoms include
fatigue, skepticism, and decreased personal and professional efficacy (Shanafelt et al., 2012;
Sorenson et al., 2016). These resulting symptoms resemble those of posttraumatic stress disorder
(NCTSN, n.d.-b).
Creative activities are defined as activities that include the personal creation of art, music,
dance, poetry, crafts, etc.
Creativity is defined as a positive concept of imagination, invention, and innovation
facilitating the development of an individual’s personality, attachments, and resolution of
challenges in novel ways (Arnout & Almoied, 2020; H. Gardner, 1982).
Resilience can be defined as the ability to adapt in positive ways to adverse or traumatic
experiences (Baskin & Bartlett, 2021).

Feasibility
The feasibility of this study relied upon access to the following: a population of mental
health providers who worked during COVID-19; relevant and valid instruments to measure
creativity and resilience; access to and knowledge of survey distribution, data collection, and
statistical computation programs; guidance and mentoring from a committee of experts;
Saybrook University Institutional Review Board (IRB) approval for study (#1019); and personal
time and capacity for the study. I had approval to access the population through various affiliate
groups from the National Child Traumatic Stress Network (NCTSN, n.d.-a), social media
recruitment, and mental health provider listservs. I received permission from the developers of
the Reisman Diagnostic Creativity Assessment (RDCA) and the Connor-Davidson Resilience
Scale 25(CD-RISC-25) to measure creativity and resilience respectively (Connor & Davidson,
2003; Reisman et al., 2016). Conducting this research relied on the reflexivity of mental health
providers to reflect on their experiences during COVID-19, as well as on their current creativity
and resilience following the pandemic. The temporality of COVID-19 also presented a
limitation, as the research questions were critical and dependent on the positionality of mental
health providers within 6 months of the end of the federal public health emergency period, May
11, 2023.
Significance of the Study
The findings from this study may assist providers in identifying creativity as a resilience
factor to combat secondary traumatic stress. The relationships revealed in this study could inform
future research, building an evidence base for creativity that could contribute to resiliency and
the reduction of secondary traumatic stress in mental health providers. Determining creativity
factors that build resiliency can lead to more specific interventions for the well-being of mental

health providers, possibly changing the manner in which organizational leaders promote
employee well-being, and the sustainability of the work force. A healthier workforce can address
the growing mental health needs of the nation.
As I reviewed existing literature, there is a gap in the literature related to this study of the
predictive relationship between creativity and resiliency in mental health providers who have
consistently managed VUCA environments. Published literature specifically focusing on
COVID19 as a VUCA environment was limited. There was a lack of published research
addressing secondary traumatic stress and burnout in mental health providers. Instead, the
published research focused on medical providers, specifically nurses.
Summary
In this chapter, the correlational study was introduced, focusing on the relationship
between creativity and resilience in mental health providers who experienced VUCA during the
federal public health emergency period of the COVID-19 pandemic. The discussion of the
problem statement was introduced within the context of my research stance outlining my role as
a mental health provider and leader during COVID-19. The description of the problem
introduced the emergence of the COVID-19 pandemic as a VUCA environment resulting in the
overwhelm and secondary traumatic stress of mental health providers. The purpose of the study
was discussed in relation to the role of creativity fostering resilience in mental health providers,
and the research questions were delineated. The predictive, exploratory correlational design
introduced the research method with a technique of surveying mental health providers in the
United States as the population. The theoretical framework of VUCA, professional quality of
life, creativity, and resilience were established, as well as definitions for concepts. Study
feasibility outlined access to population and instrumentation, including support for research

implementation. The significance of the research focused on developing creativity as a factor in
resilience which could contribute to combatting secondary traumatic stress and developing a
healthier workforce of mental health providers.
In Chapter 2, the literature reviewed includes a description of the search strategy, the
theoretical foundation, and the literature forming the theoretical framework. A critique of the
common methods and techniques used in the published studies follows. Gaps in the literature are
discussed in relation to the research questions and the focus of the study. The literature review
concludes with a summary of theories presented.

CHAPTER 2: LITERATURE REVIEW
The purpose of this study was to examine the relationship between creativity and
resilience in mental health providers working in the United States who experienced VUCA
during the federal public health emergency period of the COVID-19 pandemic (January 31,
2020–May 11, 2023) using a quantitative, predictive correlational design. The goal was to
determine the relationship between creativity and resilience and identify relevant factors that
contribute to resiliency which can mitigate secondary traumatic stress symptoms in mental health
providers. Chapter 2 includes a description of the search strategy, a discussion of the theoretical
foundation, and an analysis and synthesis of the historical and current literature about the
theoretical framework, the variables, the population, and the setting. The literature review is
composed of literature on the topic, theories, research questions, variables, population, and
setting. The theoretical framework is based on theories of VUCA, professional quality of life,
resilience, and creativity. A methodological critique of the common methods and techniques used
in the body of research described in the literature will follow. Gaps in the literature will be
discussed as pertinent to research questions and the focus of the study. The literature review
concludes with a summary of the themes and concepts presented.
Literature Search Strategy
For the purposes of this dissertation study, I reviewed relevant, scholarly, peer-reviewed
literature focusing on studies published within the last 5 years. Foundational theories of VUCA,
professional quality of life, secondary traumatic stress, resilience, and creativity were searched
using a wider time range to account for landmark studies and to create context for the study. The
summary of the literature source types and publication years are listed in Table 1.
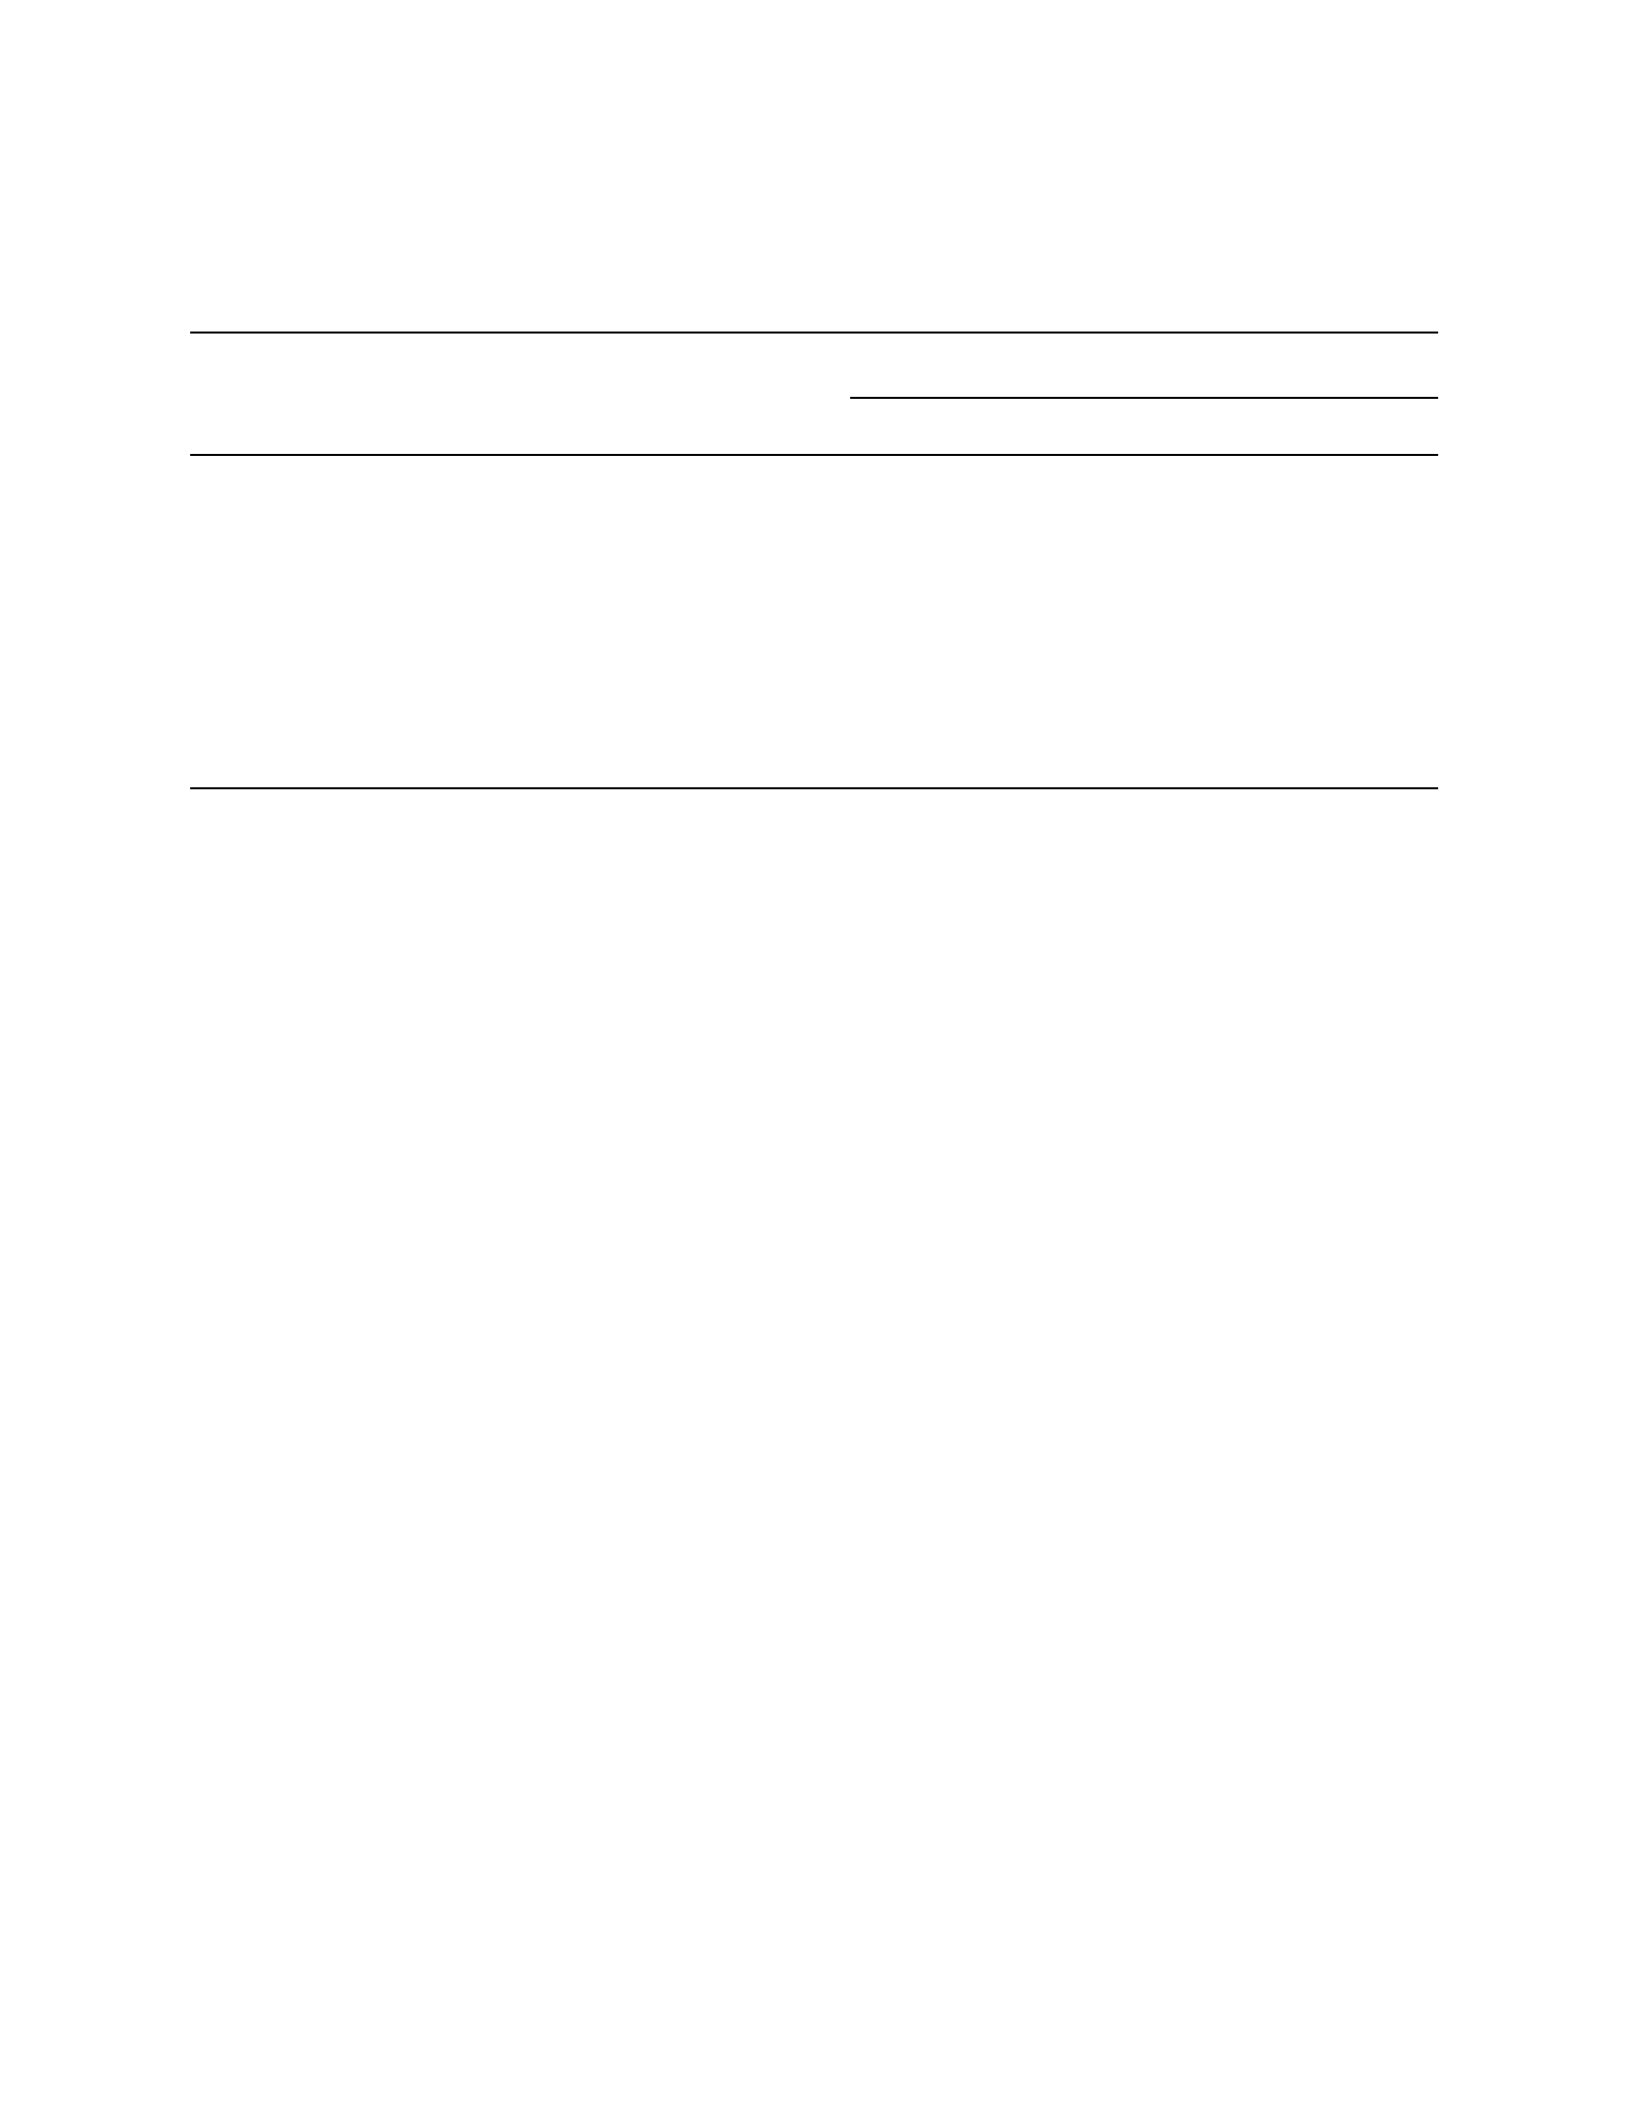
Table 1
Summary of Sources
Source type
< 2019 2019–2024
# % # %
Scholarly books 11 12.1 3 3.3
Peer-reviewed journals 23 25.3 46 50.5
Other journals or periodicals 0 0.0 1 1.1
Reports 4 4.4 2 2.2
Videos 1 1.1 0 0.0
Total 39 42.9 52 57.1
Initial search terms included mental health providers, volatility, uncertainty, complexity,
ambiguity, VUCA, secondary traumatic stress, compassion fatigue, burnout, moral injury,
institutional betrayal, creativity, creation, innovation, resilience, creative resilience, COVID,
COVID-19, COVID-19 pandemic. As my study evolved, I included related terminology relevant
to my topic and method, including creativity and resiliency measures, correlational research
strategies, and quantitative statistical analysis. The latter literature supported my choice and
approach to analysis.
The following online databases were used to search the relevant literature: BobCAT,
EBSCO Discovery Services (EDS), ERIC (EBSCO), Google Scholar, JAMA, JAMA Network
Open, Medline via PubNet, ProQuest Central, ProQuest One Academic, PsycINFO, PsycNET,
Pubmed, and SAGE Journals. I searched websites containing related information on the research
topic, including the Centers for Disease Control and Prevention (cdc.gov) and the World Health
Organization (who.int).
Theoretical Foundation
The theoretical framework for this study is based on the theories of VUCA and the
COVID-19 pandemic as a volatile, uncertain, complex, and ambiguous environment. Research
on the impact of COVID-19 on the U.S. medical system, and more specifically on the
professional quality of life of mental health care workers, is delineated using theories of
compassion satisfaction, compassion fatigue, secondary traumatic stress, burnout, institutional
betrayal, and moral injury. Strategies to ameliorate the impact of VUCA are discussed in relation
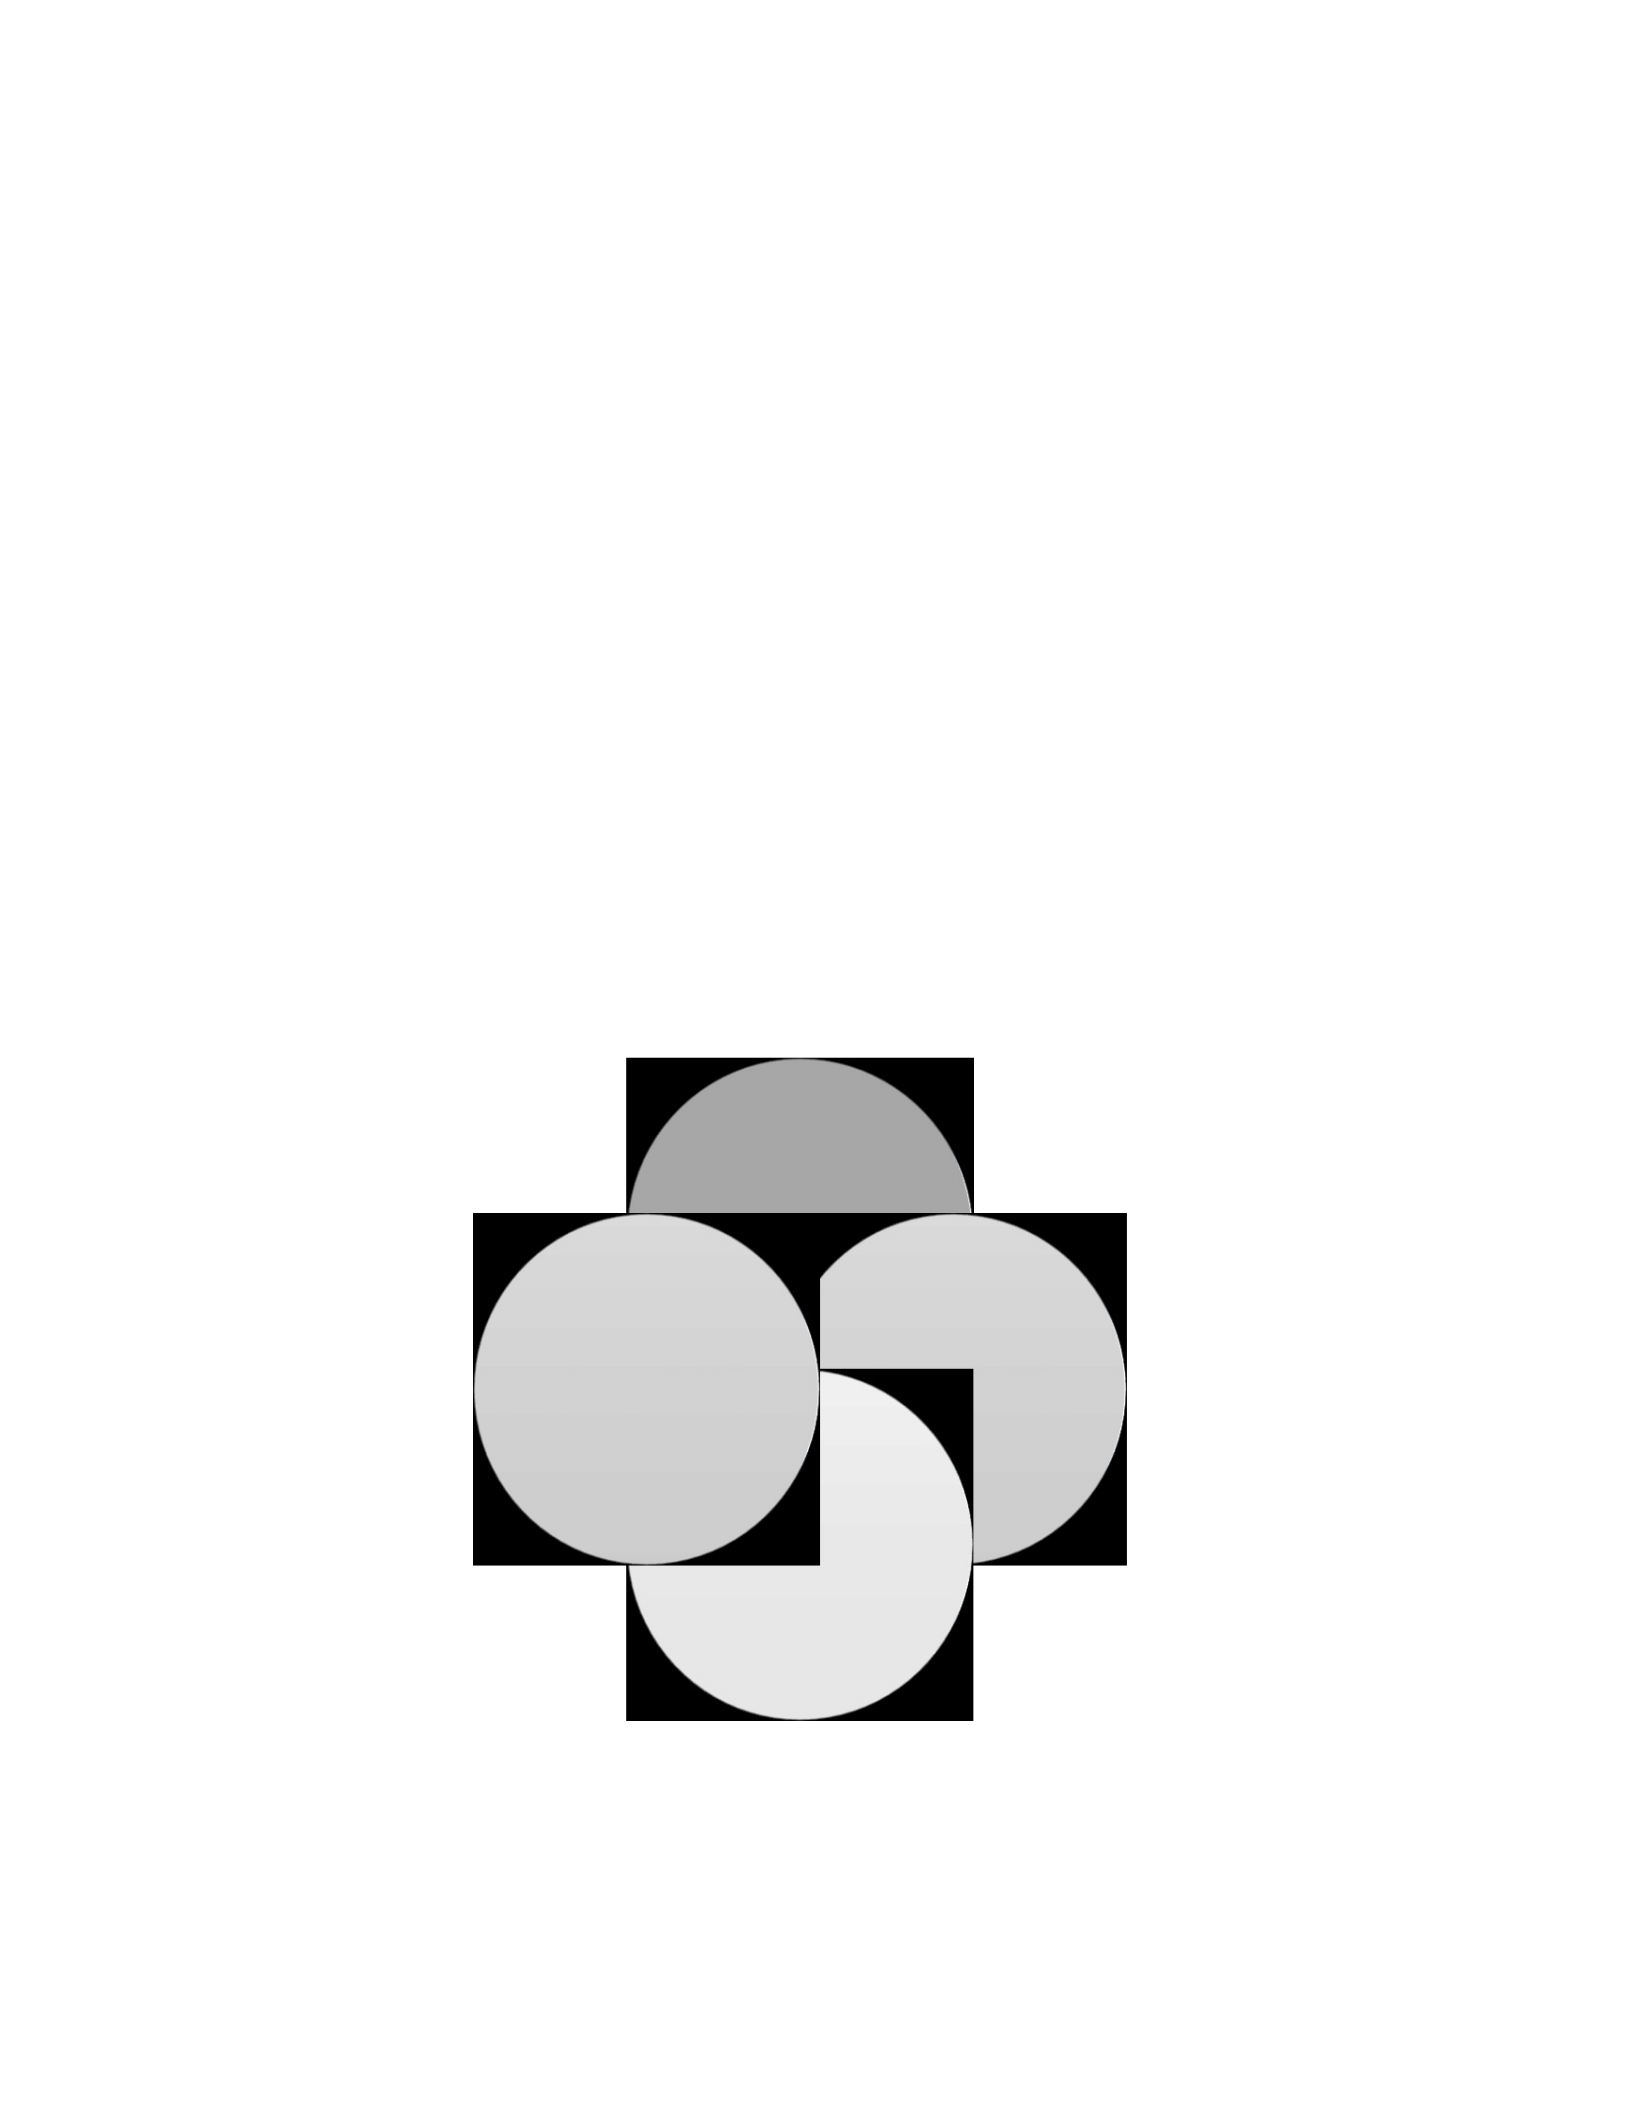
to resilience and creativity. The theoretical foundation of VUCA and COVID-19, professional
quality of life, creativity, and resilience is illustrated in Figure 1.
Figure 1
Theoretical Foundation Concept Map
Note. Relationship among foundational theories presented in a Venn diagram.
VUCA & COVID -19
Resilience
Professional Quality
of Life
Creativity

VUCA Environments
The concept of VUCA originated in the mid-1980s with the U.S. military, referring to the
geo-political instability present following the end of the Cold War (Bennis & Nanus, 1985; Dima
et al., 2021). VUCA, an acronym for volatile, uncertain, complex, and ambiguous environments,
has been used to describe these four distinct challenges and has provided language for
researchers to understand and gain perspective on the emerging landscape (Lehrner, 2021). The
first element within VUCA is volatility. The term is pertinent to instability and the likelihood that
factors can change quickly and significantly (Dziak, 2023; Lehrner, 2021). The second element
of VUCA is uncertainty, referring to the unpredictability of environments and outcomes despite
any amount of predictive research. No one can know for certain what will happen next or the
exact outcome of an action or decision. The third element in VUCA is complexity, a concept that
ties together the elements of VUCA, referring to something being difficult to understand or
control. The final element of VUCA is ambiguity. Ambiguity, or unclearness, refers to any
situation where there is a lack of clarity or relationship among factors making it impossible to
predict the outcome or effect (Dziak, 2023; Lehrner, 2021).
Taskan et al. (2022) conducted a systematic review of the literature to create a conceptual
map for factors of VUCA. The aim of the study was to define the constructs of VUCA through an
analysis of the existing literature from 1999, as this was the emergence date of VUCA-related
studies. A total of 833 relevant studies were identified through 2021, and of those, 26 studies
were chosen, as they met the criteria as peer-reviewed studies and addressed all factors of VUCA
in the study design (Taskan et al., 2022). The majority of studies were published between 2017
and 2021 within organizational systems. A concept-mapping framework was utilized to show the
link between VUCA factors identified across studies. The resulting concept map of VUCA (see
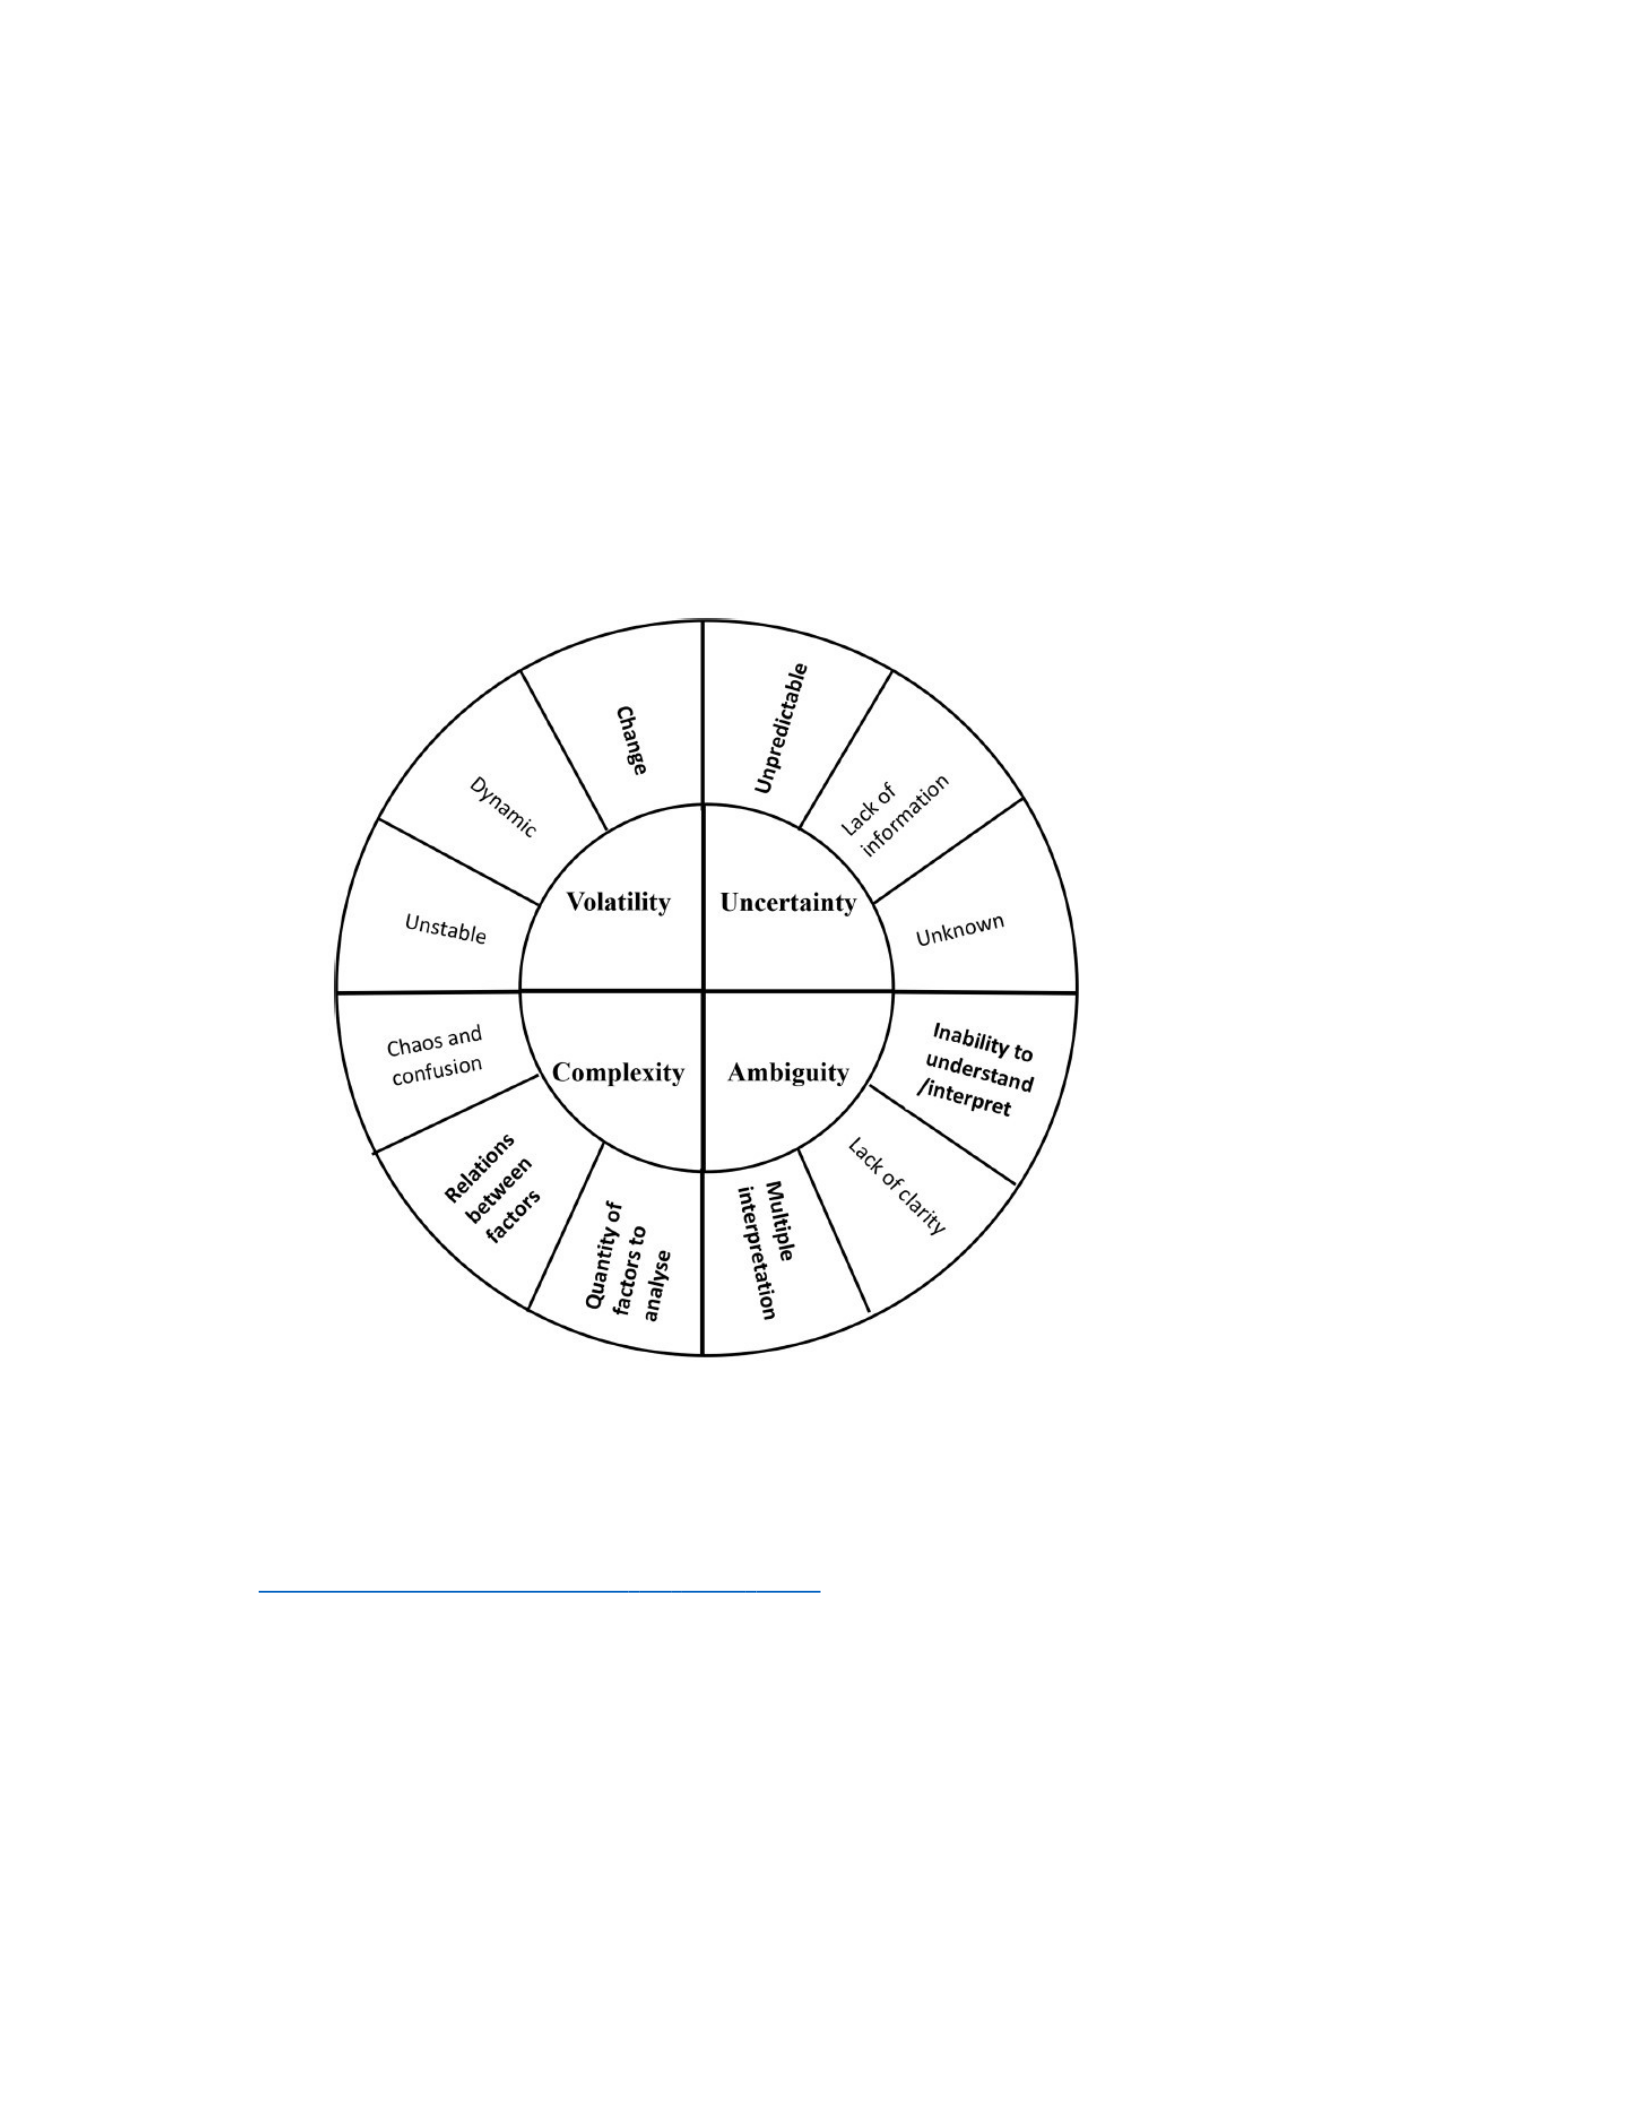
Figure 2) delineates components and could serve as a guide for forthcoming practice and
research (Taskan et al., 2022).
Figure 2
Conceptual Map of the Acronym VUCA
Note. From “Clarifying the Conceptual Map of VUCA: A Systematic Review,” by B. Taskan, A.
Junça-Silva, and A. Caetano, 2022, International Journal of Organizational Analysis, 30(7), p.
213 (https://doi.org/10.1108/IJOA - 02 - 2022 - 3136 ). CC BY 4.0.

Impact of VUCA Environments
The majority of research on the setting and impact of VUCA environments has focused
on organizational systems and leaders (Alkhaldi et al., 2017a; Brendel et al., 2016; Krauter,
2019). Examples of research conducted within a VUCA setting include the work of Brendel et al.
(2016) and Krauter (2019). The concept of VUCA was investigated in a quasi-experimental study
design of a sample of 41 business leaders in the Minneapolis area (Brendel et al., 2016). A study
of the personal quality of leaders—managing anxiety, creativity, resilience, coping with stress,
and tolerance for ambiguity, seen as successful leadership strategies in managing uncertainty—
lacked a clear delineation of how VUCA environments impacted leaders or if leaders were
currently working in a VUCA setting (Brendel et al., 2016). The assumption was that all leaders
were affected by the demands of modern organizations and the complexity of the economy,
technology, and globalization (Brendel et al., 2016). One group received leadershipbased
cognitive behavioral skills and the other group received mindfulness interventions (Brendel et
al., 2016). Both groups completed the same survey of 68 questions measuring state/ trait anxiety
and mindfulness, tolerance for ambiguity, perceived stress, and stages of change. Mindfulness
participants showed a greater change between pre- and postvalues than the leadership group in
trait anxiety, t(32) = 2.88, p = .007, and perceived stress, t(16) = 2.18, p = .018. Mindfulness
participants showed a decrease in trait anxiety, t(16) = 3.35, p = .004, and an increase in
regulatory focus, t(17) = 2.62, p = .018. No significant changes were found for the leadership
group. Brendel et al. (2016) reported results of means in bar graph table format only, which are
difficult to interpret with accurate numbers. Limitations included the measure of leaders’
perceived abilities versus the measure of observed interrelational abilities; and the shortterm
intervention of mindfulness practice versus a longer-term intervention, which may have yielded

significant results in the relationship to tolerance for ambiguity and resilience (Brendel et al.,
2016).
Krauter (2019) researched how VUCA conditions affected leaders’ performance using a
quasi-experimental design. VUCA environments can be seen as a source of adversity for leaders
resulting in the experience of extreme stress and feelings of fear, struggle, and uncertainty.
Stress-related disorders, mental health issues, and personal crises can be the effect of this
adversity. A survey comprised of a self-administered, online, structured interview questionnaire
was administered to 590 leaders in Germany (Krauter, 2019). Adversity and psychological capital
were independent variables, and leaders’ task adaptive performance was the dependent variable,
which were all measured using empirically validated and existing measures. Significant results
from multiple regression analysis indicated a moderate negative correlation between adversity
and adaptive task performance and a strong positive correlation between psychological capital
and task performance (Krauter, 2019). The findings of this study support that adverse conditions,
such as VUCA, decrease leaders’ adaptive task performance and creativity; high psychological
capital increases leaders’ performance. Recommendations included more generalized population
research, longitudinal study, person-centered study of the leader, and inclusion of follower
assessments of leaders’ performance (Krauter, 2019).
The application of VUCA as a theoretical model has not been widely researched within
mental health. In the field of disaster mental health, the prevalence and magnitude of natural and
man-made disasters have been increasing in recent decades and have contributed to growing
concerns about mounting instability in global and regional economies (Alkhaldi et al., 2017a).
These growing insecurities have created VUCA environments where leadership required
reflexivity and adaptive strategies to effectively manage the complexity (Alkhaldi et al., 2017a,

2017b). It was postulated that VUCA environments were becoming the “new normal” and would
require leadership to gain perspective and maintain flexibility, collaborate and incrementally
problem-solve, listen well, and engage in divergent thinking (Alkhaldi et al., 2017a). Several
years later, the predicted normalcy of VUCA environments was actualized with the emergence of
the COVID-19 pandemic.
COVID-19 Pandemic as a VUCA Environment
VUCA has become a widely used term to describe chaotic, unpredictable, and rapidly
changing environments in organizations, businesses, education, climate change, and, most
recently, the COVID-19 pandemic (Dima et al., 2021; Murugan et al., 2020; Taskan et al., 2022).
The World Health Organization (WHO) declared the COVID-19 outbreak a global pandemic on
March 11, 2020, and it quickly developed into a VUCA environment (Lehrner, 2021; Murugan et
al., 2020; WHO, 2023). The novel coronavirus COVID-19 developed from the severe acute
respiratory syndrome coronavirus 2 (SARS-CoV-2) from initial cases resembling symptoms of
pneumonia that appeared in China in December 2019 (Murugan et al., 2020; WHO, 2023). There
was extreme volatility and fluctuation in response to COVID-19, and by the end of federal
emergency period on May 11, 2023, there were over 765 million reported positive cases and 6.9
million deaths worldwide and over 104 million reported positive cases and 1.1 million COVID19
associated deaths in the United States (Centers for Disease Control, 2023; Lehrner, 2021; WHO,
2023). Schools and businesses closed, and stay-at-home orders were enforced on national and
international levels (Murugan et al., 2020; WHO, 2023). The complexity of the pandemic
impacted all aspects of worldwide commerce, economy, and health care, creating ambiguous and
uncertain guidelines for practice (Lehrner, 2021; Murugan et al., 2020).

Unprecedented strain was placed on health care systems responding to COVID-19, a new,
unpredictable, and uncertain disease (Baskin & Bartlett, 2021). U.S. health care management was
overwhelmed and fractured, operating without collaborative leadership and resources, which
revealed inadequacies in the health care system and highlighted the disparity between public
health and mental health practices (Fish & Mittal, 2021; Halawi et al., 2020; Klest et al., 2020;
Worley & Jules, 2020). Mental health traditionally has not been a central objective of the public
health workforce, and the COVID-19 pandemic emphasized the need for an integrative system to
promote the health of clients and providers across the nation (Fish & Mittal, 2021). As VUCA
environments intensify, the need increases for supportive system structures to support leaders,
professionals, and clients in mitigating stress-related disorders and burnout (Alkhaldi et al.,
2017a; Krauter, 2019).
Professional Quality of Life
Professional quality of life refers to the negative and positive effects of work-related
stressors on helpers (Buselli et al., 2020; Stamm, 2010). Positive effects, or compassion
satisfaction, refers to the pleasure derived from providing help to others and contributing to the
good of society (Stamm, 2009). Conversely, compassion fatigue refers to the fatigue and
exhaustion experienced as a helper (Stamm, 2010). This study focused on the professional
quality of life of the mental health care workforce. The positive and negative effects of the work
will be discussed as related to compassion satisfaction, compassion fatigue, secondary traumatic
stress, burnout, institutional betrayal, and moral injury. The specific impact of COVID-19 on
mental health care providers will be discussed in subsequent sections.

Compassion Satisfaction
Compassion satisfaction, or the positive effects on professional quality of life, occurs
when satisfaction is derived from responses to traumatic or stressful events (Lluch-Sanz et al.,
2022; Stamm, 2009). The pleasure of helping others through challenging times can result in
feelings of productivity, mattering, and contributing to the greater good (Epstein et al., 2020;
Lluch-Sanz et al., 2022). Mattering refers to a provider being of value, making a difference in the
lives of clients, and fulfilling the human needs for self-efficacy, self-determination, and
belonging (Epstein et al., 2020).
Compassion Fatigue
Compassion fatigue has also been described as the cost of caring and is understood as a
common effect of clinical practice (Figley, 2002; Litam et al., 2021). Compassion fatigue and
secondary traumatic stress share similar components, and the terminology is often used
interchangeably. Stamm (2009) attempted to delineate distinctions between compassion fatigue
and burnout in her professional quality of life (ProQOL) model. Stamm (2009) implied a
distinction between the concepts by defining compassion fatigue as encompassing both
secondary traumatic stress and burnout (Epstein et al., 2020).
Secondary Traumatic Stress
The term secondary traumatic stress (STS) refers to the cumulative effect of stress on
providers who have been chronically exposed to the emotional distress of clients (Sklar et al.,
2021). Secondary traumatic stress is a natural, work-related consequence of treating traumatized
clients (Epstein et al., 2020; Figley, 2002) and emotionally burdensome to health care providers
(Kartsonaki et al., 2023). Providers affected by STS can develop acute stress symptoms
resembling posttraumatic stress disorder, including hyperarousal, avoidance, and reexperiencing

symptoms such as intrusive thoughts (Epstein et al., 2020). These symptoms are categorized as
secondary traumatic stress disorder, which is considered a more severe response than the natural
cost of caring (Epstein et al., 2020). Secondary traumatic stress and compassion fatigue are
related terms, but STS results in longer-term symptoms of isolation and exhaustion, impairing
quality of life (Kartsonaki et al., 2023).
Burnout
The term burnout was studied in conjunction with compassion fatigue, secondary
traumatic stress, and the cost of caring (Sorenson et al., 2016). Despite this common conflation
of terms, there is often a lack of clarity in the literature regarding the distinction among them,
and researchers consistently interchange nomenclature (Figley, 2002; Hopwood et al., 2017;
Sklar et al., 2021; Sorenson et al., 2016). However, there is some agreement that burnout in
health care providers is the ultimate culmination of compassion fatigue and secondary traumatic
stress symptoms, which can result in symptoms of exhaustion, cynicism, and reduced personal
and professional efficacy (Shanafelt et al., 2012; Sorenson et al., 2016). Other researchers
associated burnout with occupational stress and challenges specifically related to the workplace
(Kartsonaki et al., 2023). Burnout was associated with the lack of supportive working
environments and heavy workloads (Kartsonaki et al., 2023).
Burnout was included as an occupational phenomenon in the International Statistical
Classification of Diseases and Related Health Problems (11th ed.; ICD-11; WHO, 2019).
Research on burnout has predominantly been focused on nurses and medical doctors in health
care settings (Sexton et al., 2022; Shanafelt et al., 2019). Physicians were found to have a higher
risk for burnout and less satisfaction with work-life balance than other working adults in the
United States (Shanafelt et al., 2019).

Institutional Betrayal and Moral Injury
Mental health providers experiencing consistent feelings of disappointment and lack of
support from their leaders and institutions can lead to institutional betrayal—when a person or
provider feels betrayed by the institution they depend on (Klest et al., 2020). Health care
organizations are “moral communities—groups of people united by a common moral purpose to
promote the well-being of others” (Epstein et al., 2020, p. 146). The health care industry
represents an organization and, as such, represents the collective responsibilities of the providers
to help those in need and be of service (Brewer, 2021). The physical and psychological safety
inherent in systems safeguards the clients and providers within an ethical framework of trust
(Brewer, 2021). When this trust is violated through intentional or unintentional actions,
institutional betrayal can occur (Brewer, 2021). Depression, fear, anger, and isolation can result
from institutional betrayal, leaving providers and patients feeling vulnerable and in need of
transparency and compassion (Klest et al., 2020).
Moral injury differs from institutional betrayal in that moral injury is the result of one’s
own action against one’s ethical principles and morality, resulting in shame and guilt (Brewer,
2021). Moral injury is considered the result of the effects of institutional betrayal (Brewer,
2021).
Impact on Health Care Providers
Historically, social service agencies have been disproportionately affected by reduced
resources and funding, which contributes to organizational and leader stress (Miller et al., 2016).
Mental health care providers were historically at a higher risk for burnout, with 21–67%
reporting symptoms of burnout (Morse et al., 2012). Before the pandemic, mental health
providers were already disproportionately vulnerable to compassion fatigue and burnout due to

trait empathy and prolonged exposure to emotional strain (Rudaz et al., 2017). Providers charged
with serving vulnerable clients who are impacted by trauma, discrimination, psychopathology,
and stressors have complex responsibilities that are inherent in the role of helper (Vîrgă et al.,
2020). Exposure to professional hazards and demands of the job includes managing high
caseloads and bureaucratic systems while dealing with daily subjection to emotionally vulnerable
conditions (Vîrgă et al., 2020). These job demands create repetitive and consistent exposures to
overwhelming situations that can lead to emotional and physical exhaustion, depersonalization,
detachment, and ultimately, if unaddressed, burnout (Hopwood et al., 2017; Shanafelt et al.,
2019; Vîrgă et al., 2020).
In a mixed methods study on vicarious trauma in relationship to secondary traumatic
stress, compassion satisfaction, and burnout, 106 trauma-based social scientists completed a
38item online survey consisting of eight questions regarding trauma exposure and a validated
instrument, the ProQOL, to measure compassion satisfaction, burnout, and secondary traumatic
stress (Whitt-Woosley & Sprang, 2018). Almost 87% of participants were exposed to secondary
traumatic stress and 57.7% experienced moderate to extreme distress (Whitt-Woosley & Sprang,
2018, p. 479). Risk factors included exposure to secondary traumatic stress and long work hours.
Chew et al. (2020) conducted a systematic review of the literature, which focused on
prior infectious disease outbreaks and the impact on health care workers, during the first months
following the outbreak of COVID-19 (Chew et al., 2020). The goal was to review prior outbreaks
and determine associated risks and effective coping strategies in an effort to inform and support
current frontline workers responding to COVID-19 (Chew et al., 2020). The results revealed that
psychological responses to prior outbreak-related adversity lasted beyond the period of time that
support was provided. Symptoms the providers experienced included fear, anxiety, posttraumatic

stress, depression, frustration, anger, and burnout, as well as posttraumatic growth, resilience,
and transformation. Internal coping resources such as problem solving and positive thinking, and
external resources such as safety, support, recognition, and communication, helped reduce
symptoms of outbreak-related stress and burnout (Chew et al.,
2020).
Impact of COVID-19 Pandemic on Mental Health Care Providers
The COVID-19 pandemic continues to reinforce a VUCA environment that will forever
impact our systems and society (Halawi et al., 2020). As of May 11, 2023, there had been more
than 765 million confirmed cases, including 6.93 million deaths worldwide (WHO, 2023). As of
May 11, 2023, 104 million cumulative cases and 1.1 million deaths occurred in the United States
since the outbreak (Centers for Disease Control, 2023; WHO, 2023). On May 5, 2023, the World
Health Organization ended the global public health emergency of the COVID-19 pandemic; the
United States declared the end of COVID-19 as a federal public health emergency on May 11,
2023 (Centers for Disease Control, 2023). Despite the end of the pandemic, COVID-19 is still
present in our communities and the impact on society is yet to be known (Centers for Disease
Control, 2023). As of March 14, 2024, there were more than 774 million confirmed cases,
including over 7 million deaths worldwide (WHO, 2023).
During the pandemic, health care providers were at an increased risk of contracting
COVID-19 due to increased exposure risk (Smallwood et al., 2022). Persisting symptoms of
COVID-19 could be debilitating and last for months, interfering with the ability of health care
workers to provide services (Smallwood et al., 2022). Long-term effects include dyspnea,
reduced lung diffusion capacity, and myocardial inflammation (Smallwood et al., 2022). Fatigue,
cough, muscle and joint pain, and loss of smell and taste were reported as long-term symptoms

among hospitalized COVID patients (Cha & Baek, 2024). Long COVID symptoms persisted
after 24 months post-infection in non-hospitalized adult patients reporting fatigue, difficulty
concentrating, amnesia, and insomnia (Kim et al., 2024). The unprecedented and widespread
event of the pandemic created uncertainty and threat, which according to Porges (2020),
stimulated the human autonomic nervous system to respond to perceived danger with
physiological arousal and fight-or-flight states. Sustained autonomic arousal affects neurological,
physiological, psychological, and behavioral systems, “resulting in visceral organ dysfunction
and compromised mental health” (Porges, 2020, p. 136). The need for co-regulation and
connection to others is critical in regaining homeostasis and a sense of safety, which was
challenging during the social isolation of the pandemic (Porges, 2020).
In a survey of 137 mental health providers, 82% of providers reported that stressors from
the pandemic severely impacted their ability to treat clients, as their personal experiences were
contributing to overwhelm and burnout (Fish & Mittal, 2021, p. 15). During the COVID-19
pandemic, social workers reported lower levels of client-related burnout but higher levels of
work-setting burnout related to organizational stressors such as high workloads, uncertainty, the
ambiguity of leadership decisions, and lack of clarity and communication (Dima et al., 2021;
Zaçe et al., 2021). Inadequate staffing, exposure to patients with COVID-19, and lack of
resources contributed to provider burnout (Smallwood et al., 2023). The shortage of mental
health care providers during the pandemic created additional burdens and overwhelm for
providers (Fish & Mittal, 2021). For mental health care providers, there was an immediate shift
to providing telehealth services, fundamentally challenging traditional and accustomed in-person
treatment delivery (Fish & Mittal, 2021).

The quickly changing landscape necessitated mental health care providers to make
adaptations that reduced transmission of the infection while simultaneously enabling them to
provide critical mental health services (Sklar et al., 2021). In addition to implementing
widespread use of telehealth and resulting telehealth fatigue, changes were needed to access
services, including modifying laws and regulations regarding privacy and confidentiality across
state lines and funding for services, which required flexibility and problem solving (Fish &
Mittal, 2021; Sklar et al., 2021). Clinicians reported that they were unprepared for these shifts
and felt overwhelmed and frustrated by the lack of boundaries separating work life from home
life (Fish & Mittal, 2021).
Personal stressors in the lives of mental health care providers were simultaneously
occurring while they provided clinical services, negatively impacting their mental health (Fish &
Mittal, 2021). The lack of social connection and the uncertainty surrounding social restrictions
also contributed to provider stress (Labrague, 2021). A survey of mental health providers
working during COVID-19 in the midwestern United States revealed a relationship between
changes in work-related tasks, settings, and team assignments and burnout among mental health
providers, resulting in turnover (Sklar et al., 2021). Recommendations to providers included
increased organizational support and trust from organizations to increase provider sustainability
(Sklar et al., 2021).
A convergent mixed-method study involved applying a VUCA framework to social work
providers in Romania responding to the unprecedented challenges that emerged during the
COVID-19 pandemic, consequent personal and job-related stressors, and burnout (Dima et al.,
2021). Dima et al. (2021) conducted a survey of 82 social workers, collecting quantitative and
qualitative data via a validated burnout inventory and open-ended questions pertinent to the

challenges experienced during COVID-19. Social workers experienced a high level of perceived
stress and burnout regarding organizational factors, such as unclear and unpredictable
expectations of workers, longer work hours, the uncertainty of best practice interventions during
this unprecedented time, and social isolation from supportive group practices (Dima et al., 2021).
Social workers reported challenges experienced during the pandemic as a lack of support from
managers, telehealth service delivery, and restrictions imposed by the agency, such as mask
wearing and social distancing (Dima et al., 2021).
A correlational study on the relationships between stress, coping response, posttraumatic
stress, and resilience predicted compassion satisfaction, secondary traumatic stress, and burnout
(Litam et al., 2021). The sample was comprised of 161 mental health counselors working in the
United States during the COVID-19. The results from correlational analysis revealed a strong
positive relationship between resilience and compassion fatigue, and a strong negative
relationship between resilience and burnout (Litam et al., 2021). Counselors working during
COVID-19 encountered higher levels of adversity, stress, and posttraumatic symptoms that
affected their professional and personal quality of life. One recommendation based on the
findings was that counselors should increase compassion satisfaction through cultivating
resilience and coping strategies, including mind-body-spirit self-care practices and lifestyle
wellness routines.
Resilience
Resilience is defined as the ability to adapt in positive ways to adverse or traumatic
experiences (Baskin & Bartlett, 2021). The capacity for resilience depends on agility, or the
ability to respond quickly and adapt to changing situations (Leask & Ruggunan, 2021).
Resilience can also be defined as a specific form of adaptation (Metzl & Morrell, 2008). This

concept can be extrapolated from an individual to a system/environmental level, where resiliency
can refer to the overall adaptability of the workforce. Resilience was found to minimize burnout
and compassion fatigue in mental health counselors, highlighting the need for policymakers to
improve provider resilience (Arnout & Almoied, 2020). To build resiliency in health care and
combat the issues of institutional betrayal and burnout, providers need support and compassion
(Klest et al., 2020;
Shanafelt et al., 2012). The organizational structure “holds” the shared experiences of the
providers, including stress, fatigue, and burnout, making self-care and resilience building a
shared responsibility. Personal self-care strategies to ameliorate burnout are often seen as the
individual provider’s responsibility and not the culture of the organization (Naehrig et al., 2021;
Shanafelt & Noseworthy, 2017). Yet, the culture of the organization is “created by the people
inhabiting it” (Hougaard & Carter, 2018, p. 161) and is shaped by their thoughts, feelings, and
behaviors. Self-care is not just a self issue but a system issue. As such, organizational leaders
have the responsibility to place people first and acknowledge the crisis of burnout in their
organizations (Hougaard & Carter, 2018; Shanafelt & Noseworthy, 2017).
Key organizational factors that contribute to workplace self-care include manager support
and awareness of compassion fatigue in mitigating burnout (Hunsaker et al., 2015). Research
conducted at the Mayo Clinic further identified organizational strategies of shared responsibility,
awareness, engagement, flexibility, community, and self-care in preventing burnout and building
resilience (Shanafelt & Noseworthy, 2017). Multi-modal service delivery and training to
reinforce and strengthen mental health providers’ resilience were also indicated (Fish & Mittal,
2021).

Polychronicity, the ability to perform multiple tasks simultaneously, correlated with
employee resilience and employee creativity among nurses (Anser et al., 2022). Inherent in the
job function of nurses is the need to manage multiple demands within a complex and changing
environment. Resiliency was seen as a mitigating factor in employee creativity and
polychronicity. A non-experimental, correlational study of 197 doctors and 358 nurses, with a
survey consisting of valid instruments for polychronicity, employee resilience, and employee
creativity, revealed that employee polychronicity had a strong, positive correlation with
creativity; employee polychronicity strongly, positively correlated with resilience; employee
resilience predicted employee creativity; and employee resilience bridged the connection
between employee polychronicity and employee creativity (Anser et al., 2022).
The relationship between employees’ agility and resiliency was investigated in a study in
South Africa during the COVID-19 pandemic (Leask & Ruggunan, 2021). A cross-sectional
survey design was used in the study with a sample of 229 respondents, yielding a final sample
size of 185 once data were cleaned. A four-part survey comprised of demographics, standardized
measure (Employee Agility and Resilience Scale), and psychometric questions revealed
significant findings related to gender and age with agility and resilience (Leask & Ruggunan,
2021). Women engaged in less self-care than their male counterparts, and participants aged 36–
45 years were more agile than those aged 56–65 years (Leask & Ruggunan, 2021). Results
indicated moderate positive correlations between resilience and collaboration, collaboration and
agility, and agility and resilience (Leask & Ruggunan, 2021).
The goal of an integrative review of 31 articles was to identify resilience in health care
workers during COVID-19 (Baskin & Bartlett, 2021). Researchers used the Connor-Davidson
Resilience Scale 25 (CD-RISC-25) in 50% of these studies to measure resilience in an

international sample of health care providers. As noted in earlier studies, survey results yielded
an inverse relationship between resilience and burnout. Nurses reported lower resilience scores
than other health care providers, and nurses with higher resilience scores reported less anxiety,
depression, and posttraumatic stress disorder (Baskin & Bartlett, 2021).
A cross-sectional study of nurses working in Iran during COVID-19 was conducted to
determine the relationship between resiliency and secondary traumatic stress (Abdolkarimi et al.,
2022). Using the CD-RISC-25 and the Secondary Traumatic Stress Scale (STSS), the
relationship between variables indicated a significant and inverse relationship between resilience
and secondary traumatic stress. Abdolkarimi et al. (2022) recommended that organizations create
programs to increase resilience and decrease stress in health care workers.
To generate a reliable and quantifiable method for measuring resilience, Connor and
Davidson (2003) created a resilience scale, the CD-RISC-25. The CD-RISC-25 is composed of a
25-item ordinal scale, measuring resilience using a 5-point Likert-type scale of 0–4. The scale
responses include choices of 0 (not true at all), 1 (rarely true), 2 (sometimes true), 3 (often true),
and 4 (true nearly all of the time). The scale is rated based on how the subject has felt over the
past month. The total score ranges from 0–100, with higher scores reflecting greater resilience
(Connor & Davidson, 2003, p. 78). In the U.S. general population, the median score was 82, with
quartiles being Q1 0–73, Q2 74–82, Q3 83–90, and Q4 91–100 (Connor & Davidson, 2003). In a
national survey of U.S. physicians in 2021, the total mean CD-RISC-25 score was 72.41 (SD =
12.1) which was equivalent to Q1, bottom 25th percentile of the general population (Nituica et
al., 2021). Data analysis consisted of descriptive statistics, internal consistency using Cronbach’s
alpha, an exploratory factor analysis, and an ANOVA. The scale demonstrated strong
psychometric properties with internal consistency, test-retest reliability, and validity (Connor &

Davidson, 2003). This scale is relevant to the current study in that it was developed from several
pertinent aspects of resilience including hardiness, coping, adaptability/flexibility,
meaningfulness/purpose, optimism, regulation of emotion and cognition, and self-efficacy
(Connor & Davidson, 2003). Limitations may include the inability to identify the source of
stressors contributing to resilience, as well as difficulty attributing resiliency to VUCA and
COVID-related stressors.
Resilience in VUCA Environments
VUCA environments are unpredictable, quickly changing, and difficult to anticipate,
which can result in a failure to plan appropriately (Brendel et al., 2016). The complexity of
events can be confusing, creating ambiguity with no clear path to resolution, which can cause
reactionary behaviors rather than thoughtful, planned actions (Brendel et al., 2016).
A positive adaptation model using the modified acronym for VUCA to delineate
strategies to combat VUCA consists of (V) vision, (U) understanding, (C) clarity, and (A) agility
(Dima et al., 2021). Vision allows for the understanding of uncertainty and does not refer to
predicting the future but rather how creating routines and acting on a personal, group, and system
level can “foster a sense of stability” (Dima et al., 2021, p. 19). Dima et al. (2021) posed that
leaders should be understanding, as it promotes accountability, openness, and trust. Clarity
around these objectives is needed to make sense of chaos and to establish expectations and
flexibility. The notion of agility relates to the ability to adapt and change quickly with flexibility,
insight, and openness (Bywater & Lewis, 2019; Dima et al., 2021). Competencies of agility
within a VUCA environment can be delineated as context-setting agility, interpersonal or
stakeholder agility, creative agility, and self-leadership agility (Joiner & Josephs, 2006). Context-
setting agility refers to the ability of one to observe and respond to their environments and take

relevant action for the desired outcome. Stakeholder agility refers to engaging stakeholders to
support and collaborate in the process. Creative agility refers to the transformation of problems
into needed results. Self-leadership agility refers to the development of personality and
leadership traits through the process of initiative and action (Bywater &
Lewis, 2019).
Mental health providers face numerous challenges within VUCA environments. To thrive
in such environments, providers must possess personal and interpersonal qualities of creativity,
resilience, stress regulation, anxiety reduction, and tolerance for ambiguity (Brendel et al., 2016;
Merrotsy, 2013). When mental health providers can tolerate ambiguity; and not become
consumed by anxiety and fear, creativity and learning can emerge (Skjei, 2014). Cultivating
tolerance for ambiguity can facilitate flexibility and innovation, critical skills needed to cope
with change (Brendel et al., 2016). Health care environments that fostered creativity and the
contributions of others were found to have more successful outcomes (Davis, 2018) and the
flexibility and innovation needed to navigate uncertainty (Arnout & Almoied, 2020; Hougaard &
Carter, 2018).
Resilience in the COVID-19 Pandemic
The ability to navigate uncertainty has been at the center of resilience research and is one
of the central themes of the COVID-19 pandemic. The construct of resilience was researched
during the early stages of the pandemic within the framework of crisis leadership and its effect
on leaders in school settings (McLeod & Dulsky, 2021). During times of crisis, resilience
contributed to learning and trust building, notable crisis management skills (Behnke & Eckhard,
2022). Improvisation was found to be a factor of resilience with leaders facing adversity in the
hospitality industry during the pandemic (Lombardi et al., 2021). Researching the relationship of

leaders with resilience during times of VUCA can provide insight into the skills needed to
survive adversity and develop competencies (Dyer, 2022).
Creativity
Creativity is linked to resilience, tolerance for ambiguity, agility, and adaptation (Joiner,
2019; Wang et al., 2011; Worley & Jules, 2020; Zenasni et al., 2008). Change is constant in a
VUCA world, and the concept of creative agility has been posed as a critical skill needed to
transform problems utilizing both creative and critical thinking (Bywater & Lewis, 2019; Joiner,
2019; Worley & Jules, 2020). As individuals become more agile, their ability to adapt to
changing environments and expectations improves, allowing for sustained change (Batool et al.,
2022; Worley & Jules, 2020).
Creativity improves presence, awareness, and “insight and self-understanding”
(GoslinJones & Herron, 2016, p. 199). A uniquely human trait, creativity fosters flexibility,
adjustment to life, openness, and courage (Cropley, 2020; May, 1975). Creativity can be seen as
the drive
“behind all growth and development” (Cropley, 2020, p. 358) contributing to adaptation and
innovation. Creativity is defined as a positive construct of innovation and imagination enabling
an individual to develop personality, improve relationships, and problem solve in novel ways
(Arnout & Almoied, 2020; H. Gardner, 1982). Indicators of creativity include cognitive
flexibility, divergent thinking; tolerance for risks and ambiguity, curiosity, motivation, and
learning (Arnout & Almoied, 2020; Mumford & Todd, 2019; Reisman et al., 2016). Efforts to
measure creativity have been challenging, resulting in a wide variety of measures and
taxonomies aimed at capturing trait, ability, behavior, process, and product creativity, as well as
domains of innovation, thinking, and problem-solving (Weiss et al., 2021). There is no unified

definition of creativity within the research, nor a universal assessment measure; therefore,
interpretation of creativity is defined by each individual researcher (Glăveanu & Kaufman, 2020;
Kapoor & Kaufman, 2020; Weiss et al., 2021).
Creativity can be further defined through a set of factors related to “fluency, flexibility,
elaboration, originality, resistance to premature closing, tolerance of ambiguity, convergent and
divergent thinking, risk taking, and intrinsic motivation and extrinsic motivation” (Reisman et
al., 2016, p. 177). The Reisman Diagnostic Creativity Assessment (RDCA; Reisman et al., 2016)
is a 40-item, Likert-type format self-report measure that is designed to assess the creative
strengths of an individual. The RDCA has advantages, which include the accessibility of the
selfreport design and the universal method of the Likert scale for survey data collection, which
allows for familiarity and comprehension (Black, 1999; Reisman et al., 2016). Cronbach’s alphas
fell between > .6 and ˂ .9 demonstrating strength in reliability and internal consistency for the
measure (Black, 1999; Reisman et al., 2016). Scoring ranges from 0–240, with 0–95 indicating
very low creativity, 96–119 indicating low creativity, 120–143 indicating average creativity, 144–
203 indicating moderately high creativity, and 204–240 indicating very high creativity (Reisman
et al., 2016).
Creativity was investigated in workplace settings. In a study of 172 nurses in Pakistan,
the relationship between authentic leaders and creativity, mediated by resiliency, was
investigated (Anwar et al., 2020). Surveys completed by nurses measured authentic leadership,
hope, resilience, and creativity. Results of the study revealed that authentic leadership developed
hope in nurses, hope mediated the relationship between creativity and authentic leadership, and
resiliency contributed to workplace creativity in nurses (Anwar et al., 2020). In the hotel industry
in Malaysia, a cross-sectional study was conducted which examined the effects of indirect

“servant leadership on organistional [sic] sustainability (OS) through creativity and
psychological resilience” (Batool et al., 2022, p. 71). Results yielded a significant positive
relationship between creativity and organizational sustainability and between psychological
resilience and organizational stability (Batool et al., 2022). Creativity was viewed as a renewable
human resource that was central to sustainability and ecological modeling. Further qualities of
resilience were defined as flexibility, consistency, tolerance, and perseverance (Batool et al.,
2022).
Gratitude and resilience contributed to work-related well-being and creativity, as
discovered in a study of 610 psychological counselors (Arnout & Almoied, 2020). Structural
equation modeling was used to examine how resilience, gratitude, and well-being could predict
creativity (Arnout & Almoied, 2020). The hypothesized model showed goodness of fit for
resilience, gratitude, and well-being predicting creativity. Recommendations to increase
counselors’ gratitude and resilience through agency-based training were a means to increase
work-based creativity, satisfaction, and effectiveness in counseling and therapy (Arnout &
Almoied, 2020).
During the social isolation of the COVID-19 pandemic, creativity served as a method for
meaning-making, and creative activities were found to reduce the impact of current stressors and
contribute to overall well-being (Elisondo, 2021; Kapoor & Kaufman, 2020). In a mixed method,
longitudinal study of people living in Argentina during COVID-19, emotions were analyzed in
relation “to the development of creative activities” (Elisondo, 2021, p. 118). In the first phase,
305 people were surveyed using an online questionnaire of demographics, emotions, and creative
activities during isolation. In the second phase, 20 people participated in semi-structured
interviews with questions pertaining to daily activities, creative processes, and new activities

they engaged in during social isolation. Descriptive statistics and qualitative thematic coding
were utilized in the analysis. Thematic definitions of terms for resiliency, stress, emotion, and
well-being were used, and descriptive coding was used to categorize participants’ responses.
Most participants indicated the experience of positive emotions during creative activities, as well
as the time to engage in creative activities during the isolation of COVID-19. Negative emotions
were also reported in relation to work and financial challenges. Results indicated that creative
activities contributed to well-being during the isolation of the pandemic.
During times of uncertainty and adversity, crisis becomes the stable dimension (Weston
& Imas, 2018). As things are in a constant state of change, instability both heightens and
highlights one’s awareness of their environment (Weston & Imas, 2018). Crisis can trigger action
and propel one to seek creative solutions to navigate adversity. The concept of adversity capital
addresses how creativity and innovation can foster one’s resilience to adapt and survive during
times of sustained hardship (Weston & Imas, 2018). Essentially, creativity becomes a mechanism
for survival. Hunter et al. (2019) and May (1975) have discussed creativity as courage, as it is
within the limits that one faces that creativity rises, giving way to creative resilience. Richards
(2007) further contended that in the tasks of everyday life, creativity emerges as improvisation
and adaptation to challenges.
The concept of creative resilience was not evident in pandemic-related literature but
appeared in the literature related to cultural globalization research (Coutu, 2002; Dunn, 2020).
Creative resilience was conceptualized from the adaptation from colonialism by indigenous
peoples as a “process of resistance, survival, and adaptation in the face of past or prevailing
adversity, social trauma and tragedy” (Dunn, 2020, p. 6). Resilience comes from the act of
creating solutions from thin air when facing adversity (Dunn, 2020). To date, creativity as a

predictive factor of resilience does not appear in the pandemic-related literature, which creates an
opportunity for the current study to contribute to the field of resilience in health care providers.
Methodological Review
Within the last year, research on COVID-19 as a VUCA environment has been published
creating a direct link to a theoretical foundation for this study (Lehrner, 2021; Murugan et al.,
2020). Over the last few years, the literature on resilience and creativity in managing the
COVID-19 pandemic has expanded, with a focus on adaptive coping versus symptom awareness
(Anser et al., 2022; Anwar et al., 2020; Elisondo, 2021). The exploration of factors that influence
resiliency, rather than just identifying the problem, has emerged. The impact of creativity on
resiliency is limited in published studies to date (Anser et al., 2022), a notable theme within this
study’s construct, but there is correlational research focused on resilience affecting creativity
(Arnout & Almoied, 2020). The following methodological review will contain common methods
and techniques used in the body of research presented in this chapter and the strengths and
weaknesses regarding the research designs, population and sampling methods, data collection,
and data analysis.
Research Design
The majority of studies focused on VUCA environments, reflecting the application of a
situational correlation (Brendel et al., 2016; Dima et al., 2021; Krauter, 2019; Litam et al., 2021)
or assumed VUCA environment (Alkhaldi et al., 2017a, 2017b) rather than examining VUCA as
a construct (Taskan et al., 2022). However, in one study, each factor of VUCA was individually
addressed, delineating characteristics of volatility, uncertainty, complexity, and ambiguity
(Taskan et al., 2022). This approach allowed for a specific research design and application of the
individualized VUCA factors (Black, 1999; Taskan et al., 2022).

Several studies involved the application of quasi-experimental design to examine the
concept of VUCA as their setting (Brendel et al., 2016; Krauter, 2019). In quasi-experimental
design, randomization is not utilized and therefore can be considered a weakness (Schweizer et
al., 2016). However, this approach allows for population-specific sampling and is less expensive
than experimental studies, allowing for real-world applications and generalizability (Schweizer et
al., 2016). The majority of the studies involved the application of a descriptive correlational
design (Anser et al., 2022; Demir, 2018; Leask & Ruggunan, 2021), which allows for the
analysis of relationship strength between variables but cannot predict causality between variables
(Black, 1999). The lack of a cause-and-effect relationship is a weakness of correlational design
(Black, 1999).
Population and Sampling Methods
The majority of the literature reviewed in this chapter focused on settings in health care
(Sorenson et al., 2016) and business (Alkhaldi et al., 2017a; Brendel et al., 2016; Krauter, 2019),
with less research focusing on education (McLeod & Dulsky, 2021). Populations that were
investigated consisted of mainly medical providers (doctors and nurses) and leaders in business
and health care, but also included mental health providers (Fish & Mittal, 2021; Litam et al.,
2021; Rudaz et al., 2017; Sklar et al., 2021; Vîrgă et al., 2020), teachers, and social scientists
(Whitt-Woosley & Sprang, 2018).
Sampling methods included snowball, cluster, random, census, and non-judgmental
sampling techniques. Cluster sampling techniques provide a feasible approach to gaining
population representation, yet high error rates and implicit bias are common weaknesses (Black,
1999; Demir, 2018). Population sampling procedures used in a study with 172 nurses yielded a
homogenous group, with respondents representing single, female, young adults with an average

of 3 years of work experience (Anwar et al., 2020). The results of Anwar et al.’s (2020) study
cannot be generalized to the larger nursing population due to these controls, presenting a
weakness in this study (Black, 1999). Methodological strengths of Anwar et al.’s (2020) study
included surveys being administered in successive 15-day intervals, at the same time and
location to reduce common method bias (Anwar et al., 2020; Black, 1999). Large sample sizes
and power analysis to determine the minimal response rate needed for survey completion
strengthen the validity of a study (Black, 1999).
Data Collection
Data collection predominantly included surveys consisting of self-administered, online,
structured interview questionnaires, as seen in studies by Anser et al. (2022), Anwar et al. (2020),
and Leask and Ruggunan (2021). Self-administered questionnaires are accessible and easy to
distribute; disadvantages of self-report measures can include the respondent’s subjective and
individual bias and emotional state at the time of completion, as well as effort to satisfy the
assessor (Black, 1999). Surveys consisting of validated and reliable instruments and questions
strengthen the internal rigor of the design (Black, 1999; Field, 2018). In a study, 106 social
scientists were surveyed using a 38-item online survey consisting of eight questions pertinent to
trauma exposure and a validated instrument, the ProQOL, that measured compassion satisfaction,
burnout, and secondary traumatic stress (Whitt-Woosley & Sprang, 2018). The ProQOL is a
widely used, validated, and reliable instrument, but there was no disclosure regarding validity or
reliability testing on the eight trauma-based questions; therefore, it is not possible to determine
the efficacy of those questions (Black, 1999; Whitt-Woosley & Sprang, 2018). A Cronbach’s
alpha should have been used to demonstrate the internal validity and reliability of the constructs
strengthening methodological design (Black, 1999).

Data Analysis
Descriptive and inferential statistics were used to analyze most survey/questionnaire data.
Demographic variables were analyzed using descriptive statistics employing a combination of
nonparametric and parametric statistical analysis (Black, 1999; Field, 2018). Two studies
involved regression analysis data in the form of tables and discussed the meaning of relationships
in response to their hypotheses (Anser et al., 2022; Krauter, 2019). The analysis method included
correlation matrix, regression (multivariate), confirmatory factor analysis, and descriptive
analysis (Anser et al., 2022; Krauter, 2019).
Regression analysis using ordinary least squares was used in one study (Leask &
Ruggunan, 2021), and partial least squares structural equation modeling (PLS-SEM) was used to
test for common method variance by Batool et al. (2022). Methodological strengths included the
detailed description of the method and specific data in the form of tables, concept maps, and data
visualization, which provided the ability for replication of the study (Batool et al., 2022; Black,
1999). Structural equation modeling (SEM) was used in several studies for the analysis of
variables rather than multi-variate regression, allowing for a comparative approach to variable
relationships (Anser et al., 2022; Brendel et al., 2016; Demir, 2018; Tomarken & Waller, 2005).
In summary, the methodological review yielded common themes in quantitative design
across studies. In the majority of the studies, researchers utilized correlational analysis,
descriptive statistics, and regression analysis. Structural equation modeling (Batool et al., 2022;
Demir, 2018) and factor analysis (Anser et al., 2022; Connor & Davidson, 2003; Reisman et al.,
2016) were also used as successful quantitative designs and allowed for multi-variable and
multirelational analysis (Black, 1999). Sampling included snowball, cluster, population, and
nonprobability methods.

Gaps in the Literature
As I have investigated my research question and existing literature, there appears to be a
gap in the literature about the resiliency and creativity of mental health providers who have
consistently adapted to VUCA environments. There is a scarcity of published research on the
relationship between creativity and resilience. Despite the presence of creativity in the literature,
there is a shortage of research in mental health viewing creativity as a predictive variable for
resilience. The predictive relationship is evident between resilience and creativity in published
studies (Anser et al., 2022; Anwar et al., 2020; Arnout & Almoied, 2020); however, there was no
discussion as to how creativity has a predictive relationship with resilience. Claims of creativity
informing resilience were evident from an opinion perspective, but there is a lack of published
quantifiable studies investigating these claims (Dunn, 2020).
The result of the review of the literature indicates a lack of published research addressing
the role of creativity in navigating VUCA environments and the impact on mental health
workers. Published research focuses on medical providers and burnout, specifically nurses.
Published literature specifically focused on COVID-19 as a VUCA environment is limited.
Summary and Conclusions
The emergence of COVID-19 as a VUCA environment has affected the overall wellbeing
of mental health providers. As the pandemic emerged as a volatile, uncertain, complex, and
ambiguous environment (VUCA), unpredictability strained health care systems, creating
instability (Baskin & Bartlett, 2021). Mental health care providers were adversely affected by the
COVID-19 pandemic, and they needed to adapt rapidly to provide needed services (Fish &

Mittal, 2021; Sklar et al., 2021). These conditions led to an increase in secondary traumatic stress
symptoms and burnout in mental health providers who were already disproportionately
vulnerable due to job-related stressors as a helper (Vîrgă et al., 2020).
Resilience, a form of positive adaptation to stressors, can ameliorate the impact of
secondary traumatic stress, compassion fatigue, and burnout (Arnout & Almoied, 2020; Metzl &
Morrell, 2008). Positive adaptation, as seen in the VUCA model of vision, understanding, clarity,
and agility, promotes stability, flexibility, and insight (Bywater & Lewis, 2019; Dima et al.,
2021). Flexibility and tolerance for ambiguity are key factors that assist one in navigating and
coping with uncertainty and change, allowing for creativity to emerge (Arnout & Almoied, 2020;
Brendel et al., 2016; Skjei, 2014).
Creativity fosters flexibility and adjustment to uncertainty (Cropley, 2020). Creative
agility is a critical factor in adapting to the changing environments of a VUCA world (Batool et
al., 2022; Worley & Jules, 2020). The intersection of creativity and resilience contributes to
overall wellbeing, meaning-making, and adaptation to adversity (Arnout & Almoied, 2020;
Dunn, 2020; Kapoor & Kaufman, 2020).
The factors of resilience and creativity are the central variables in the current study. In
reviewing the common methods of research design, correlational and structural equation
modeling were evident in several (Anser et al., 2022; Brendel et al., 2016; Demir, 2018).
Survey/questionnaire data collection were the most common techniques used across studies.
Analyses included paired t tests, Pearson’s correlations, Mann-Whitney U, and nonparametric
statistics as common methods for analyzing data.
The purpose of this research study was to examine the relationship between creativity and
resilience in mental health providers who experienced VUCA during the COVID-19 pandemic

using a quantitative predictive correlational design. The goal of this study was to determine the
relationship between creativity and resilience and identify relevant factors that contribute to
resiliency, which can mitigate secondary traumatic stress symptoms in mental health providers.
In Chapter 3, the method of the current study will be discussed, including the purpose, research
questions, design, population, sampling method, variables, and instrumentation. This chapter
incorporates data collection, data analysis procedures, and rigor, and concludes with
ethical considerations and a summary.

CHAPTER 3: METHODOLOGY
This chapter contains the purpose of the study and the research questions for clarity and
consistency. Subsections include the research design, population and sampling method, variables,
and instrumentation. This section incorporates data collection, data analysis procedures, and
rigor, and concludes with ethical considerations and a summary. This research study was
approved by the Saybrook Institutional Review Board on June 21, 2022.
Purpose of the Study
The purpose of the quantitative predictive correlational study was to examine the
predictive relationship between creativity and resilience in mental health providers who
experienced VUCA while working in the United States during the federal public health
emergency period of the COVID-19 pandemic. The COVID-19 federal public health emergency
is defined as the period of time which ranged from January 31, 2020, through May 11, 2023 (Silk
et al., 2023). The goal of this study was to determine the relationship between creativity and
resilience and identify relevant factors that contribute to resiliency, which can mitigate secondary
traumatic stress symptoms in mental health providers.
Research Questions and Hypotheses
R1: What is the predictive relationship between creativity and resilience in mental health
providers who experienced VUCA during the federal public health emergency period of the
COVID-19 pandemic?
H10: There is no predictive relationship between creativity and resilience.
H1a: There is a predictive relationship between creativity and resilience.
R2: What is the predictive relationship between task creativity and resilience in mental
health care providers who engaged in creative activities during the federal public health
emergency period of the COVID-19 pandemic?

H20: There is no predictive relationship between engaging in creative activities and
resilience.
H2a: There is a predictive relationship between engaging in creative activities and
resilience.
R3: What is the predictive relationship between professional quality of life and resilience
in mental health care providers who experienced VUCA during the federal public health
emergency period of the COVID-19 pandemic?
H30: There is no predictive relationship between professional quality of life and
resilience.
H3a: There is a predictive relationship between professional quality of life and resilience.
R4: To what extent does secondary traumatic stress moderate the relationship between
creativity and resilience in mental health care providers who experienced VUCA during the
federal public health emergency period of the COVID-19 pandemic?
H40: Secondary traumatic stress does not moderate the relationship between creativity
and resilience.
H4a: Secondary traumatic stress does moderate the relationship between creativity and
resilience.
A sufficient sample size was not obtained to conduct research question 5.
R5: Which factors of creativity predict resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic?
H50: No factors of creativity predict resilience.
H5a: One or more factors of creativity predict resilience.

R6: Which subfactors of creativity predict resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic?
H60: No subfactors of creativity predict resilience.
H6a: One or more subfactors of creativity predict resilience.
Research Design
The foundation of this dissertation was quantitative, as quantitative research allowed for
the examination of relationships between creativity and resilience. Quantitative research within
the social sciences is defined as an investigation into a problem by collecting numerical data to
explain, predict, confirm, or validate relationships among variables (Leedy & Ormrod, 2019).
Quantitative social science appeared in the mid-1950s in response to the impressionistic
treatment of historical election results through a narrative, biographical lens and called for a
quantifiable approach that analyzed patterns within and in relation to other elections to expand
definition and context of social and political history (Anderson, 2007). Procedures for statistical
analysis expanded in the 1960s with mainframe computing and led way to landmark studies,
such as research by Curti et al. (1959) where data analysis of archival census data was combined
with qualitative historical records, challenging conventional wisdom of the time.
For this study, a correlational research method was used. The analysis of relationships
among variables, correlational research, was first postulated by Galvin in 1875, which led to the
conceptualization of linear regression and the Pearson product-moment correlation (PPMC;
Stanton, 2001). Through a predictive, exploratory correlational design, I examined the
association and predictive relationships through the administration of an online survey and
analysis of the responses.

In correlational studies, the researcher has no control over the variables; however, one
variable may be used to predict another variable (Black, 1999). I used the data to establish a
model that demonstrates the variable of creativity predicting resilience, which required
parametric and nonparametric bivariate correlational and regression analyses (Black, 1999;
O’Connel, 2006). The findings from this study regarding which interrelationships exist among
variables can promote future practice and research into causality (Black, 1999).
Population and Sampling Method
The target population was mental health practitioners providing mental health services in
the United States during the COVID-19 federal public health emergency period from January 31,
2020, through May 11, 2023. Mental health practitioners were defined as providers working
directly or indirectly with clients to provide mental health services. Mental health services
consist of interventions of treatment, assessment, diagnosis, counseling, direct service support,
policy, and administration in public, private, outpatient, or inpatient settings for mental and
behavioral disorders.
Selection criteria for inclusion were: (a) working directly or indirectly with clients; (b)
providing mental health services consisting of interventions of treatment, assessment, diagnosis,
counseling, direct service support, policy, and administration in public, private, outpatient, or
inpatient settings for mental and behavioral disorders; (c) working in the United States; and (d)
having worked for any duration of time during the COVID-19 federal public health emergency
period from January 31, 2020, through May 11, 2023.
Exclusion criteria were: (a) working in a job where primary duties are not mental health
specific (such as a general medical provider, first responder, teacher, etc.); (b) working outside of

the United States; and (c) not having worked for any period of time during the COVID-19 federal
public health emergency period from January 31, 2020, through May 11, 2023.
The population was sampled from mental health practitioners working in the United
States from the NCTSN, social media recruitment, and mental health provider listservs at the end
of the federal public health emergency period, between July 6, 2023, and September 12, 2023.
The NCTSN is administered by SAMHSA and is coordinated by UCLA-Duke University
National Center for Child Traumatic Stress (NCCTS; NCTSN, n.d.-a.). The NCTSN is a network
of hundreds of mental health agencies and programs with thousands of practitioners across the
United States that serve children and families who have experienced trauma. This population was
clearly defined and was a good fit for the research questions, which reduced population-specific
bias (Daniel, 2012). I gained a memo of understanding from the NCCTS to gain access to the
population through affiliate group contacts. I am a member of the NCTSN, and due to the
extensive membership of the network, I did not have personal relationships with the participants
that may have affected their participation. Objectivity is central to collecting unbiased data and
for researchers to remain detached from participants during the study (Leedy & Ormrod, 2019).
To mitigate this influence on participation, data collection was anonymous, with waiver of
documentation of informed consent. Informed consent outlined measures for study participation
(Bracken-Roche et al., 2017) and was appended online via acknowledgement of agreement of the
terms of consent.
The participants were practitioners, and the information pertained to their well-being.
There were minimal risks involved in this study, as the participants were not considered a
vulnerable population. To mitigate risk associated with participation in the study, all participants
received an informed consent outlining specific risks and disadvantages (Bracken-Roche et al.,

2017). Additional risks included the time to complete the survey; heightened awareness to
personal traits, experiences regarding secondary traumatic stress, professional quality of life,
resiliency, and creativity; anxiety or distress related to questions during or following data
collection; a previously unknown risk or side effect; and/or a potential breach of confidentiality.
The informed consent also included benefits of participation, which may have increased survey
completion (Bracken-Roche et al., 2017). Benefits included participants gaining greater insight
into their perceived and actual creativity and resilience, which may affect their sense of wellness.
Participants contributed to research that aimed to identify protective factors against secondary
traumatic stress, which may lead to helping themselves and other mental health providers. A free
provider self-care exercise was offered as an incentive upon completion of the survey (see
Appendix A).
To further maximize response rate, I conducted a census and snowball sampling approach
from the targeted population of providers (Black, 1999; Daniel, 2012). As this group represented
a small, heterogenous, sub-population, it was important to capture characteristics inherent within
the population, which merited a census sampling approach (Daniel, 2012). Large samples
representative of a specific population enhance generalizability (Leedy & Ormrod, 2019). A
census approach to sampling eliminated random sampling errors and selection bias because a
sample of the population was not collected (Daniel, 2012). A sample size of 171 participants was
attained, which was not sufficient to support additional analyses, such as stepwise or ordinal
logistic regressions, which require a larger sample size to produce credible results (Daniel, 2012).
For research question 1, a bivariate analysis using a Pearson correlation was used
requiring a sample size of 83. An a priori sample size was calculated by using G*Power3 with a

power = .80, a medium effect size, two-tails, and standard alpha error of 0.05 (Faul et al., 2007).
The sample size required for a linear multiple regression analysis was calculated by using
G*Power3 with a power = .80, a medium effect size (0.15), two-tails, standard alpha error of
0.05, and one predictor (Faul et al., 2007). The a priori analysis for linear multiple regression
yielded the needed sample size of 55.
For research questions 2, 3 and 6, a Spearman’s rho was used requiring a sample size of
95. Because Spearman’s rank correlation coefficient is computationally identical to Pearson
product-moment coefficient, power analysis was conducted using the same G*Power 3 a priori
sample size calculation as research question 1 (Faul et al., 2007; Field, 2018). However, due to
nonparametric tests being less robust than parametric tests, the sample size was increased by
15% to detect a significant relationship, if one exists (Fahoome, 2002). The a priori analysis for
linear multiple regression yielded the needed sample size of 55.
For research question 4, a moderation analysis was used requiring a sample size of 55.
The sample size required for a moderation multiple regression analysis was calculated by using
G*Power3 with a power = .80, a medium effect size (0.15), standard alpha error of 0.05, one
tested predictor, and three total predictors (Faul et al., 2007).
Recruitment resulted in an insufficient sample size to support ordinal logistic regression
or stepwise regression analyses required for research question 5. The a priori sample size for
ordinal logistic regression was calculated by using G*Power3 with a power = .80, a medium
effect size (0.15), standard alpha error of 0.05, two-tails, and odds ratio of 1.3, yielding the
needed sample size of 477 (Faul et al., 2007). The a priori sample size for stepwise hierarchical
multiple regression was calculated using a medium effect size (0.15), with a power = .80,

standard alpha error of 0.05, 40 predictors in set A, and 25 predictors in set B, yielding a needed
sample size of 212 (Soper, 2023).
Based on the a priori sample size calculation, I planned to survey at least 95 participants
using the demographics of gender identity, age, race/ethnicity, professional training/background,
role, setting, years in practice, and affiliations. The resulting data collection yielded 171
participants.
Variables and Instrumentation
For this study, creativity was considered the predictor variable and was measured using a
standardized instrument comprised of ordinal responses (Reisman et al., 2016). The criterion
variable, resilience, was measured using a standardized instrument of ordinal responses (Connor
& Davidson, 2003). The predictor variable, creativity, is measured by the RDCA, a Likert-type
scale instrument with a summative score (Reisman et al., 2016). The ordinal criterion variable of
my study is resilience, as measured by the CD-RISC-25, a Likert-type scale instrument with a
summative score (Connor & Davidson, 2003). These instruments are described below.
Instrumentation
Study variable data was collected using validated instruments on creativity, as measured
by the Reisman Diagnostic Creativity Assessment (RDCA) and resilience, as measured by the
Connor-Davidson Resilience Scale 25 (CD-RISC-25; Connor & Davidson, 2003; Reisman et al.,
2016). The RDCA is a summative score measure based on 40 statements rated on a 6-point
Likert-type scale ranging from strongly disagree to strongly agree (Reisman et al., 2016). The
RDCA is a validated self-report measure that is based on a summative score of 0–240, with a
higher number associated with greater creativity (Reisman et al., 2016). Cronbach’s alphas fell
between > .6 and ˂ .9, demonstrating strength in reliability and internal consistency for the

measure (Black, 1999; Reisman et al., 2016). Subfactors of the RDCA consist of summed items
and include originality, fluency, flexibility, elaboration, tolerance for ambiguity, resistance to
premature closing, divergent thinking, convergent thinking, risk-taking, intrinsic motivation, and
extrinsic motivation (Reisman et al., 2016). These subfactors consist of relevant groupings of
related questions from the RDCA. Factor definition consists of the following: originality as
“unique and novel”; fluency as “generates many ideas”; flexibility as “generates many categories
of ideas”; elaboration as “adds details”; tolerance of ambiguity as “comfortable with the
unknown”; resistance to premature closing as “keeps an open mind”; divergent thinking as
“generates many solutions”; convergent thinking as “comes to closure”; risk-taking as
“adventuresome”; intrinsic motivation as “inner drive”; and extrinsic motivation as “needs
reward or reinforcement” (Reisman et al., 2016, pp. 181–182).
The CD-RISC-25 is a validated, self-report measure that consists of 25 items rated on a 5-
point Likert-type scale ranging from 0–4 with a total summed score of 0–100; a higher number is
associated with greater resilience (Connor & Davidson, 2003). Data analysis consisted of
descriptive statistics, internal consistency using the Cronbach’s alpha, an exploratory factor
analysis, and an ANOVA. The scale demonstrated strong psychometric properties with internal
consistency, test-retest reliability, and validity (Connor & Davidson, 2003). Individual items from
the CD-RISC-25 and RDCA should be treated as ordinal data (Connor & Davidson, 2003; P. L.
Gardner, 1996; Neuman, 2011; Reisman et al., 2016).
Since the summed score of both the CD-RISC-25 and the RDCA can be continuous from
absolute 0–100 or 0–240 respectively, with equal intervals, and there was precedence for treating
the summed scores as continuous scale data, the data was treated as ratio data (Connor &
Davidson, 2003; NurseKillam, 2014; Reisman et al., 2016).
Permission was obtained for both the RDCA and the CD-RISC-25 from the developers in
April 2022 via emailed documentation. The RDCA and the CD-RISC-25 were free to use. The
developers relinquished rights to any data collected during this study.
Variables of VUCA, professional quality of life, secondary traumatic stress, and task
creativity were considered as variables and moderators of the relationship and were measured via
participants’ responses to Likert-type responses to statements. Data were collected from
participants on separate Likert-type statements pertaining to variables of VUCA, professional
quality of life (positive and negative), secondary traumatic stress, and task creativity. Variable 1,
VUCA, was measured using the response to the following statements: “I experienced volatility
during the emergency period of the COVID-19 pandemic”; “I experienced uncertainty during the
emergency period of the COVID-19 pandemic”; “I experienced complexity during the
emergency period of the COVID-19 pandemic”; and “I experienced ambiguity during the
emergency period of the COVID-19 pandemic.” Participants rated VUCA statements using 1
(strongly disagree), 2 (moderately disagree), 3 (mildly disagree), 4 (mildly agree), 5 (moderately
agree), and 6 (strongly agree). Variable 2, professional quality of life, was measured using the
response to the following statements: “My professional quality of life was positively affected
during the emergency period of the COVID-19 pandemic”; and “My professional quality of life
was negatively affected during the emergency period of the COVID-19 pandemic.” Participants
rated quality of life statements using: 1 (never), 2 (rarely), 3 (occasionally), 4 (frequently), and 5
(very frequently). Variable 3, secondary traumatic stress, was measured using the response to the
statement, “I experienced secondary traumatic stress during the emergency period of the
COVID-19 pandemic”. Participants rated secondary traumatic stress statements using: 1 (never),
2 (rarely), 3 (occasionally), 4 (frequently), and 5 (very frequently). Variable 4, task creativity,

was measured using the response to the statement, “I engaged in creative activities during the
emergency period of the COVID-19 pandemic, such as personal creation of art, music, dance,
poetry, crafts, etc.” Participants responded to task creativity statements using: 1 (never), 2
(rarely), 3 (occasionally), 4 (frequently), and 5 (very frequently).
Likert-type data are based on relative positions of attitudes and assumptions that are
unequally distributed and therefore are treated as ordinal data (Arnold et al., 1967; NurseKillam,
2014). The value of the interval is unknown, and nonnumeric traits are used to capture feelings,
judgments, and assumptions (Black, 1999).
Demographics
Gender identity is nominal, with response choices categorized into the following groups:
female, male, non-binary/third gender, transgender, cisgender, agender, genderqueer, I prefer to
self-identify, I prefer not to answer, or none of the above (NurseKillam, 2014). Age was
collected as ordinal, with age ranges in the following categories: 18–25, 26–39, 40–54, 55–64,
and 65 and older (NurseKillam, 2014). Race/ethnicity is nominal, with response choices
categorized as: African American/Black, Alaska Native, American Arab/Middle Eastern/North
African, American Indian, Asian/Asian American, biracial/multiracial,
Hispanic/Latin(a/o/e)/Latinx, Native Hawaiian/other Pacific Islander, White, I prefer to
selfidentify, I prefer not to answer, or none of the above. Professional training/background is
nominal, with response choices categorized in the following subgroups: medical doctor, nurse or
nurse practitioner, licensed doctoral-level psychotherapist, licensed MA/MSW-level
counselor/therapist, graduate/internship doctoral-level therapist trainee, graduate/internship
MA/MSW-level therapist trainee, unlicensed agency-employed therapist/counselor, BA/MAlevel
case manager, frontline BA-level mental health/child welfare/juvenile justice program/agency

staff, BA/MA-level psychometric assessor, peer-to-peer counselor, or other, please specify. Role
is nominal, with response choices categorized into the following groups: administrator (e.g.,
executive, project, clinical, or service director); case manager; caseworker supervisor; child
welfare worker; clinic coordinator or manager; clinical supervisor; clinician; creative arts
therapist; evaluator; expert through lived experience; faculty; frontline worker/direct service
professional; or other, please specify (NurseKillam, 2014). Setting is nominal, with response
choices categorized into the following groups: public or private psychiatric hospital; nonfederal
general hospital with separate psychiatric unit; U.S. Department of Veterans Affairs medical
center; residential treatment center for children and adults; community mental health center;
outpatient, day treatment, or partial hospitalization mental health facility; university/ college; or
private practice (NurseKillam, 2014). Years in practice were collected as ordinal year ranges in
the following categories: 1–5 years, 6–10 years, 11–15 years, 16+ years. Ordinal data do not
have standardized and equal interval scales but do allow for a relative ranking of data points
(Black, 1999). NCTSN affiliation is nominal, with response choices categorized into the
following groups: I am not a member of the NCTSN; Category I; Category II; Category III;
Individual affiliate; Organizational affiliate; Family partner; Young adult partner; Community
partner; SAMHSA staff; don’t know; and other, please specify.
The combined questions from the demographics, Likert-type items, and the
instrumentation formed the survey questionnaire. To establish face validity for the Likert-type
data consisting of questions about VUCA, professional quality of life, secondary traumatic stress,
and task creativity, the questionnaire was distributed to content experts for review (Collingridge,
2023). Once reviewed, a psychometrician examined the questionnaire to check for errors and

clarity (Collingridge, 2023). To assess internal consistency reliability for the Likerttype data, a
Cronbach’s alpha was calculated for the various categories of items resulting in α =
.733. The α coefficient was between 0.65 and 0.8, demonstrating consistency and reliability
(Tavakol & Dennick, 2011).
Data Collection
Data collection consisted of a survey/questionnaire technique distributed through email to
the target population of mental health providers within 4 months after the end of the pandemic
emergency period, May 11, 2023. Participants were recruited in the United States from the
NCTSN, email contacts, mental health provider listservs, and social media recruitment on
Facebook and LinkedIn. Participants were sent an invitation through email or social media post
describing the research. For those interested in participating, a URL link to the informed consent
was provided where participants clicked to accept consent for participation. The informed
consent was not signed, participation was anonymous, and IP addresses were not recorded. If the
individual declined participation, they closed the email. Once a participant clicked to indicate
agreement with the terms of consent, the survey loaded (see Appendix B). The survey was
webbased, using Qualtrics for ease of collection and data entry. A CAPTCHA question was
included at the beginning of the survey to prevent automated bots from completing the survey.
Surveys are commonly used in correlational research with instruments to collect data on
multiple variables within each subject (Black, 1999). The one-time, single survey form consisted
of demographics and variables pertinent to experiences during the federal public health
emergency period of COVID-19; the survey included existing, validated instruments: the
Reisman Diagnostic Creativity Assessment (RDCA) to measure creativity (Reisman et al., 2016)

and the Connor-Davidson Resilience Scale 25 (CD-RISC-25) (Connor & Davidson, 2003) to rate
resiliency.
Surveys, namely web-based surveys, have low response rates due to a variety of factors,
including concern for anonymity, inaccurate email addresses, infrequent use of email, junk mail,
viruses, and lack of understanding as to how to respond (Daniel, 2012). To minimize
nonresponse bias, the description and purpose of the research was clearly defined, which may
have increased motivation among participants to contribute to valuable research within their
respective fields (Daniel, 2012). The informed consent described how anonymity was
maintained, reducing concerns for confidentiality. To further minimize nonresponse bias, the data
collection period was lengthened with email prompts to encourage survey participation (Daniel,
2012). The methods I used to secure information included encrypting and storing digital files on
OneDrive within password protected folders and locking any paper-based materials in a locked
filing cabinet.
Data Analysis Procedures
I used Excel and SPSS 26 for data entry and analysis. A codebook was created where
each data point was assigned a code, description, and level of measurement (Kent State
University, n.d.).
Descriptive Statistics
Descriptive statistics were used to describe the sample characteristics and the variables.
Frequency counts and percentages, measures of central tendency, and dispersion were used as
appropriate to the levels of measurement of the variables. Correlation matrix, univariate analysis,
and crosstabulations were used to analyze sample characteristics. As these demographics
contained nominal and ordinal data, they required a combination of nonparametric and
parametric statistical analysis (Fox, 2018; Statistics Learning Centre, 2012).

The nominal level of measurement was used for gender identity, race/ethnicity,
professional background/training, role, and setting. Data analysis consisted of frequency
distribution and mode as a measure of central tendency, as they were appropriate tests for
nominal data and were critical in gaining an understanding of participants (Black, 1999;
NurseKillam, 2014).
The ordinal level of measurement was used for age group, year group for years in
practice, and the Likert-type data measuring the variables of VUCA, professional quality of life,
secondary traumatic stress, and task creativity. A Cronbach’s alpha was used to assess internal
consistency reliability of the Likert-type scale items (Black, 1999; Field, 2018) within each set of
items. Data analysis consisted of mode, range, frequency distribution, and coefficients of
correlation (Black, 1999; NurseKillam, 2014). Mode was a useful measure of central tendency,
as the median cannot be calculated with nominal data. The mode was the most frequent value
and is not affected by extreme values present in skewed data (Field, 2018). Determining the
range in data without extreme values can provide indication of variability (Field, 2018).
Frequency distributions or histograms were useful in assessing the properties of distribution of
scores to determine which correlation coefficient to utilize (Field, 2018). Correlation coefficients
were used to assess the direction and strength of the relationship between pairs of variables. This
was important in my study, as the Pearson correlation coefficient was used when variables were
normally distributed, and the Spearman’s rho was used when variable data were not normally
distributed (NurseKillam, 2014). The strength of the Pearson correlation coefficient and the
Spearman’s rho was interpreted, with +0.1 to +0.3 and –0.1 to –0.3 indicating weak correlation,
+0.4 to +0.6 and –0.4 to –0.6 indicating moderate correlation, +0.7 to +0.9 and –0.7 to –0.7
indicating strong correlation, and +1 to –1 indicating perfect correlation (Akoglu, 2018).

Inferential Statistics
Research Question 1
The summed score of the CD-RISC-25 and the RDCA were treated as continuous scale
data as there is precedence established (Connor & Davidson, 2003; NurseKillam, 2014; Reisman
et al., 2016). Assumptions were tested for normality, or normal distribution, using a predicted
probability plot; skewness and kurtosis were examined using a histogram; linearity (that the
predictor variables in the regression have a straight-line relationship with the outcome variable)
using correlation coefficients; and homoscedasticity using a scatterplot. In sample sizes less than
200, values between –1.96 and +1.96 for skewness and kurtosis are considered normally
distributed (Matore & Khairani, 2020). Assumptions were met for normality, linearity, and
homoscedasticity. Therefore, the Pearson correlation coefficient and a Pearson linear regression
were used, the most reliable tests to measure continuous variables (Black, 1999; Field, 2018). To
further identify how VUCA moderated the relationship between creativity and resilience, a
moderation analysis was used (Field, 2018).
Research Questions 2 and 3
To determine prediction between Likert-type statements and the CD-RISC-25, the
Spearman’s rho was used to determine bivariate correlation (Black, 1999). This nonparametric
test is appropriate to the levels of measurement. A Spearman’s rho, two-tailed, was used as a
coefficient of correlation to determine the relationship between statements, comprised of ordinal
data, and the total sum score of the CD-RISC-25, which was treated as continuous scale data
(Black, 1999; Khamis, 2008). Since there were Likert-type statement variables, a multiple
regression was used to determine predictability between each statement and resilience, as
measured by the CD-RISC-25 (Black, 1999).

Research Question 4
For research question 4, a moderation analysis was conducted to determine the interaction
effect of secondary traumatic stress on the relationship between creativity and resilience. The
moderator variable is “one that affects the relationship between two others” (Field, 2018, p. 359).
A multiple regression analysis between the summed score of the RDCA and the summed score of
the CD-RISC-25 was moderated by the variable of secondary traumatic stress (Connor &
Davidson, 2003; Reisman et al., 2016).
Research Question 5
A sufficient sample size was not attained to support using a stepwise hierarchical and/or
ordinal logistic regression analysis to test the fifth research question. This approach to analysis
would have been helpful, as it is well suited for hypothesis testing in correlational studies
involving data collected from ordinal responses from surveys with Likert-type scales (O’Connel,
2006). Having a sufficient sample size would have allowed for a factor analysis between
creativity, as measured by the RDCA, and resilience, as measured by the CD-RISC-25 (Connor
& Davidson, 2003; Reisman et al., 2016). The 40 individual items from the RDCA would have
been treated as predictor variables and the summative score of CD-RISC-25 as the dependent
variable in an ordinal logistic regression.
Research Question 6
For research question 6, a Spearman’s rho was used to determine correlation coefficients
between the 11 subscale scores and the total summed score of the CD-RISC-25 (Black, 1999).
The RDCA has subscores on 11 factors of creativity which were determined through instrument
development and were found to be reliable and valid factors (Reisman et al., 2016; Trochim,
2020). A correlational matrix was well suited for the data analysis (Black, 1999). A weighted

multiple regression was used to predict resilience, as measured by the CD-RISC-25 from the
subscale scores of the RDCA (Faul et al., 2007). Weighted regression is appropriate when data
are heteroscedastic to correct and reestimate the model (Field, 2018).
Rigor
Consistency across the study design, from the research question and hypotheses to the
data collection, assessment, and statistical analysis, is crucial to ensure rigor in the study (Leedy
& Ormrod, 2019). Standards of rigor aligned with this correlational research design include
construct validity, internal validity, external validity, and statistical conclusion validity (Black,
1999).
Construct Validity
In correlational research, construct validity is critical in ensuring that the instrument
measures what it is supposed to measure (Black, 1999). Beginning with the defined research
question and hypothesis, I have clearly defined concepts and constructs that are built upon
existing theories to create a solid foundation for the study (Black, 1999). The concepts, construct,
and operational definition have logical continuity, and the chosen instruments measure the
intended outcome (Trochim, 2020).
Threats to construct validity that are pertinent to my research design include inexact
definitions of constructs, mono-method bias, hypothesis guessing, and evaluation apprehension
(Trochim, 2020). To minimize effects of these threats, multiple considerations must be
considered, including specific, accurate, and detailed operational definitions for the concepts of
creativity and resilience, and using instruments that measure the factors identified (Trochim,
2020).

Participants may have engaged in hypothesis guessing, making assumptions as to what
was being researched and basing their responses accordingly (Trochim, 2020). This behavior
could have affected the survey results if participants assumed that higher levels of creativity
result in greater resilience. Additionally, participants may have been apprehensive about the
survey, which could result in poor performance or the desire to provide inaccurate responses in
the effort to look good (Trochim, 2020). A potential solution to minimize threats to validity
included anonymity of participants, instructions indicating there were no wrong or right answers,
and not labeling the research hypothesis in the survey instructions (Black, 1999; Trochim, 2020).
Internal Validity
Internal validity is relevant in quantitative studies where researchers attempt to establish a
causal relationship (Trochim, 2020). Reducing threats to internal validity relies upon eliminating
alternative explanations for a finding. Factors that improve internal validity include blinding,
randomization, and random selection, factors that were not possible in my research design
(Trochim, 2020). Furthermore, in correlational research, internal validity is low, since there is no
manipulation or control (Black, 1999). This survey-based descriptive correlational research
design reflected relationships naturally existing within real-world settings, thus having low
internal validity (Trochim, 2020). Other variables, known and unknown, may explain any
relationships found.
External Validity
External validity refers to the extent to which a researcher can generalize findings of a
study to other populations, settings, situations, and measures (Trochim, 2020). Factors that
strengthen external validity include a representative sample of the general population of study
that connects to the hypothesis, research design, instrumentation, data collection, and analysis

(Black, 1999). In this research, I conducted a census and snowball sampling approach to a target
population of mental health providers. As this group represented a small, heterogenous
subpopulation, it was important to capture characteristics inherent within the population, which
merited a census sampling approach (Daniel, 2012). This technique allowed for greater
generalizability to other similar populations across settings (Black, 1999). Random heterogeneity
was a possible threat, which was addressed with a larger sample size (Black, 1999). External
validity was strengthened with a cohesive plan that had a logical continuity linking operational
definitions through instrumentation and data analysis (Trochim, 2020).
Statistical Conclusion Validity
Statistical conclusion validity refers to the degree to which a researcher’s conclusions
about relationships in the data are reasonable (Trochim, 2020). Conclusion validity can be
improved by strengthening statistical power, improving reliability, and assuring good
implementation (Trochim, 2020). I addressed threats to conclusion validity in my study by using
a larger sample size and conducting a power analysis with a power =.80 and medium effect size
to generate stronger statistical power (Black, 1999; Faul et al., 2007). I used the RDCA and the
CD-RISC-25, which are existing, validated instruments that demonstrated strong psychometric
properties, with internal consistency, test-retest reliability, and validity (Price et al., 2018). A
Cronbach’s alpha demonstrated strong internal consistency reliability of the Likert-type scale
items resulting in α = .733 (Tavakol & Dennick, 2011).
Limitations and Feasibility
Limitations included uncertainty regarding the number of participants that would
complete the survey (Black, 1999; Daniel, 2012). The use of this research design relied upon a
large sample size for statistical significance (Faul et al., 2007). The sample size was sufficient to

conduct predictive analyses but was not sufficient for ordinal logistic regression (Black, 1999),
as was required for research question 5. As stated in the sampling method subsection, I am a
member of the NCTSN and may have name recognition amongst participants. Anonymity and
confidentiality of the participants addressed this potential issue (Bracken-Roche et al., 2017).
Conducting this research relied on the reflexivity of mental health providers to reflect on their
experiences during the COVID-19 federal emergency period, as well as on their experiences
following the pandemic, which were contemporaneous with survey completion. The temporality
of COVID-19 also presented a limitation, as the research questions were critical and dependent
on the positionality of mental health providers in that particular moment in time. Limitations of
correlational research exist in terms of the inability to manipulate variables and the inability to
account for other variables, known and unknown, that might explain any significant relationships
found (Field, 2018).
Summary/Conclusion
This chapter outlined the pertinent subsections of the research method to frame the
research study to ensure clarity and consistency. The chapter began with introducing the purpose
of the correlational study: to examine the relationship between creativity and resilience in mental
health providers who experienced VUCA during the federal public health emergency period of
the COVID-19 pandemic. Research questions focused on the examination of multiple
relationships among variables of VUCA, professional quality of life, secondary traumatic stress,
creativity, and resilience.
Through a predictive, exploratory correlational design, I examined the association and
predictive relationships between variables through the administration of an online survey and
analysis of the responses. The target population of mental health care providers working during

the COVID-19 pandemic were recruited from various mental health practitioner listservs and
social media platforms in the United States. A census and snowball sampling approach were used
to collect survey data from the population. The survey consisted of demographics, standardized
instruments to measure creativity and resilience, and Likert-type statements pertaining to
variables of VUCA, professional quality of life, secondary traumatic stress, and task creativity.
Analysis included descriptive and inferential statistics, including nonparametric and
parametric statistical analysis. Based on the sample size, various options for hypotheses testing
included bivariate analysis, linear regression, and weighted multiple regression. Construct
validity, internal validity, external validity, and statistical conclusion validity were discussed.
Ethical considerations including limitations, confidentiality, anonymity, and feasibility issues
were presented.
CHAPTER 4: RESULTS
The purpose of the quantitative predictive correlational study was to examine the
relationships between creativity and resilience in mental health providers who experienced
VUCA while working in the United States during the federal public health emergency period of
the COVID-19 pandemic, which began on January 31, 2020, and ended on May 11, 2023 (Silk et
al., 2023). Identifying creativity factors that contribute to resiliency can mitigate secondary
traumatic stress symptoms in mental health providers.
The contents of Chapter 4 include the research questions and hypotheses, followed by
data collection, including recruitment and characteristics of the sample, results, and data analysis.
The results are organized by study variables and hypotheses testing, which includes descriptive
and inferential statistics. The chapter concludes with a summary and introduction to Chapter 5.

Research Questions and Hypotheses
R1: What is the predictive relationship between creativity and resilience in mental health
providers who experienced VUCA during the federal public health emergency period of the
COVID-19 pandemic?
H10: There is no predictive relationship between creativity and resilience.
H1a: There is a predictive relationship between creativity and resilience.
R2: What is the predictive relationship between task creativity and resilience in mental
health care providers who engaged in creative activities during the federal public health
emergency period of the COVID-19 pandemic?
H20: There is no predictive relationship between engaging in creative activities and
resilience.
H2a: There is a predictive relationship between engaging in creative activities and
resilience.
R3: What is the predictive relationship between professional quality of life and resilience
in mental health care providers who experienced VUCA during the federal public health
emergency period of the COVID-19 pandemic?
H30: There is no predictive relationship between professional quality of life and
resilience.
H3a: There is a predictive relationship between professional quality of life and resilience.
If a sufficient sample size is obtained to support multivariate analyses, the following
research questions will be addressed through supplemental analyses.

R4: To what extent does secondary traumatic stress moderate the relationship between
creativity and resilience in mental health care providers who experienced VUCA during the
federal public health emergency period of the COVID-19 pandemic?
H40: Secondary traumatic stress does not moderate the relationship between creativity
and resilience.
H4a: Secondary traumatic stress does moderate the relationship between creativity and
resilience.
R5: Which factors of creativity predict resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic?
H50: No factors of creativity predict resilience.
H5a: One or more factors of creativity predict resilience.
R6: Which subfactors of creativity predict resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic?
H60: No subfactors of creativity predict resilience.
H6a: One or more subfactors of creativity predict resilience.
Data Collection
Data collection consisted of a survey/questionnaire technique distributed through email to
the target population of mental health providers within 2 months of the end of the pandemic
emergency period, May 11, 2023. The one-time, single survey form consisted of CAPTCHA
security, informed consent, inclusion criteria, demographics, and Likert-type statements pertinent
to experiences during the federal public health emergency period of COVID-19 regarding

VUCA, professional quality of life, secondary traumatic stress, and task creativity; existing,
validated instruments were also included: the Reisman Diagnostic Creativity Assessment
(RDCA) to measure creativity and the Connor-Davidson Resilience Scale 25(CD-RISC-25) to
rate resilience during the postpandemic emergency period.
Sampling and Recruitment
Participants were recruited in the United States from the NCTSN and other mental health
provider listservs, and through social media recruitment. Participants were mental health
practitioners who provided mental health services in the United States during the COVID-19
federal public health emergency period from January 31, 2020, through May 11, 2023. In this
research, I conducted a nonprobability, census, and snowball sampling approach to a target
population of mental health providers. Recruitment began on July 6, 2023, applying a census
sampling approach to email distribution and social media posts to LinkedIn and Facebook. In
addition to affiliate group email distribution, the administrators from the NCTSN advertised the
recruitment flyer in their monthly newsletter to the network on August 2, 2023. A snowball
sampling approach was used to further disseminate recruitment where participants were invited
to forward the email and/or social media posts to colleagues and affiliate groups. A QR code was
attached to the email and social media posts for ease of access. Social media posts were updated
and reposted weekly. An email prompt was sent as a reminder to the original distribution list on
August 22, 2023. Data collection ended at midnight on September 12, 2023, and the Qualtrics
survey link was closed.
A total of 340 individuals entered the survey link and completed the CAPTCHA security
question, and 169 individuals partially completed the survey, yielding 171 completed surveys.
Completed surveys consisted of the CAPTCHA security, informed consent, inclusion criteria,

demographics, variables regarding VUCA, professional quality of life, secondary traumatic
stress, and task creativity during the COVID-19 federal emergency period, and the RDCA and
the CD-RISC-25 instruments to measure creativity and resilience during the postpandemic
emergency period.
Characteristics of the Sample
The Department of Health and Human Services (HHS)—SAMHSA and the Health
Resources and Services Administration (HRSA)—estimated there were approximately 1.2
million behavioral health providers in the U.S. in 2020 (U. S. Government Accountability Office,
2022). Nonprobability sampling was used for this study, yielding 171 participants, which
represents .014% of the larger U.S. behavioral health population.
The results of descriptive statistical analysis of the sample’s demographic variables are
listed below in tabular format. Tables 2 through 6 reflect instances where participants may have
given more than one response to reflect their identity (N =171). The information in Table 2
displays the gender identity of participants. The mode of the sample is female, representing more
than 86% of the sample.
Table 2
Descriptive Statistics: Gender Identity of Participants
Gender identity n %
Female 150 86.2
Male 19 10.9
Non-binary/third gender 1 0.6
Transgender 0 0.0
Cisgender 0 0.0
Agender 0 0.0
Genderqueer 1 0.6
Self-identify 3 1.7
Prefer not to answer 0 0.0
Total 174 100.0
Note. N = 171. Participants could select multiple responses.
The information in Table 3 depicts the race/ethnicity of the sample with more than four
fifths of the participants identifying as White. White women were 76% of the sample and Latina
women were 9% of the sample, comprising the two largest groups in the sample.
Table 3
Descriptive Statistics: Race/Ethnicity of Participants
Race/ethnicity n %
African American/Black 5 2.7
Alaska Native 0 0.0
American Arab/Middle Eastern/North African 2 1.1
American Indian 3 1.6
Asian/Asian American 6 3.2
Biracial/multiracial 6 3.2
Hispanic/Latin(a/o/e)/Latinx 17 9.0
Native Hawaiian/other Pacific Islander 0 0.0
White 143 76.1
Self-identify 4 2.1
Prefer not to answer 0 0.0
None of the above 2 1.1
Total 188 100.0
Note. N = 171. Participants could select multiple responses.

The information in Table 4 indicates the professional background/training of participants,
with licensed MA/MSW-level counselors/therapists and licensed doctoral-level psychotherapists
representing more than 80% of the sample.
Table 4
Descriptive Statistics: Professional Background/Training of Participants
Background n %
Medical doctor 0 0.0
Nurse or nurse practitioner 2 1.1
Licensed doctoral-level psychotherapist 58 31.9
Licensed MA/MSW-level counselor/therapist 92 50.5
Graduate/internship doctoral-level therapist trainee 2 1.1
Graduate/internship MA/MSW-level therapist trainee 13 7.1
Unlicensed agency-employed therapist/counselor 4 2.2
BA/MA-level case manager 4 2.2
Frontline BA-level mental health, child welfare, juvenile
justice program/agency staff
1 0.5
BA/MA-level psychometric assessor 0 0.0
Peer-to-peer counselor 2 1.1
Other 4 2.2
Total 182 100.0
Note. N = 171. Participants could select multiple responses.
Clinicians were 34.6% of the sample, clinical supervisors were 15.1% of the sample, and
creative arts therapists were 14.6% of the sample for the largest groups. The results in Table 5
indicate the multiple perspectives/positions of the participants.
Table 5
Descriptive Statistics: Perspectives/Positions of Participants
Perspective/position n %
Administrator 38 10.9
Case manager 6 1.7
Caseworker supervisor 1 0.3
Child welfare worker 2 0.6
Clinic coordinator or manager 11 3.1
Clinical supervisor 53 15.1
Clinician 121 34.6
Creative arts therapist 51 14.6
Evaluator 4 1.1
Expert through lived experience 12 3.4
Faculty 17 4.9
Frontline worker/direct service professional 30 8.6
Other 4 1.1
Total 350 100.0
Note. N = 171. Participants could select multiple responses.
Clinicians in private practice comprised 44% of the sample, clinical supervisors in private
practice comprised 18%, and creative arts therapists in private practice comprised 16%, which
were the largest groups. The results in Table 6 reflect the multiresponses of participants
pertaining to work setting, with more than 40% of participants working in private practice,
followed by community mental health centers.
Table 6
Descriptive Statistics: Work Settings of Participants

Work setting n %
Public or private psychiatric hospital 19 8.3
Nonfederal general hospital with separate psychiatric unit 6 2.6
U.S. Department of Veterans Affairs medical center 2 0.9
Residential treatment center for children and adults 13 5.7
Community mental health center 39 17.0
Outpatient, day treatment, or partial hospitalization mental
health facility
30 13.1
University/college 28 12.2
Private practice 92 40.2
Total 229 100.0
Note. N = 171. Participants could select multiple responses.
The results in Table 7 depict the age range of participants, with most aged between 40–54
years of age, followed by 26–39 years of age. Those 18–25 years of age represent the smallest
percentage of the sample.
Table 7
Descriptive Statistics: Age Range of Participants (N = 171)
Age range n %
18–25 5 2.9
26–39 47 27.5
40–54 68 39.8
55–64 31 18.1
65 and older 20 11.7

The information in Table 8 indicates the majority of the sample has practiced for over 16
years. The mode of the sample are participants between the ages of 40–54 with over 16 years of
experience in the field.
Table 8
Descriptive Statistics: Years in Practice (N = 171)
Years in practice n %
1–5 years 28 16.4
6–10 years 28 16.4
11–15 years 41 24.0
16+ years 74 43.3
The information in Table 9 indicates that two thirds of the sample were not members of
the NCTSN. Members of the NCTSN represented 32.2% of the sample.
Table 9
Descriptive Statistics: NCTSN Membership of Participants (N = 171)
NCTSN membership n %
Not a member 116 67.8
Category I 1 0.6
Category II 17 9.9
Category III 11 6.4
Individual affiliate 12 7.0
Organizational affiliate 13 7.6
SAMHSA staff 1 0.6

Study Results
This section pertains to the results of the study beginning with the analysis of the
variables pertaining to experiences during the COVID-19 federal emergency period, including
VUCA, professional quality of life (positive and negative), secondary traumatic stress, and task
creativity. The next section includes the results of the RDCA and the CD-RISC-25 reflecting
creativity and resilience during the post pandemic period. The final section addresses the results
of hypothesis testing.
Variables Pertaining to Experiences During COVID-19 Federal Emergency Period
A Cronbach’s alpha was conducted across the Likert-type response predictor variables of
VUCA, professional quality of life (positive and negative), secondary traumatic stress, and task
creativity, which generated evidence of the internal consistency reliability (α = 0.730). The
survey questions pertaining to these predictor variables were novel and created for this research
study and were examined in relation to one another. The internal consistency reliability of the
RDCA and the CD-RISC-25 were demonstrated in prior studies.
The following tables display the descriptive results of the criterion variables of VUCA,
including frequency counts and percentages and measures of central tendency and dispersion.
The results in Table 10 indicate that the majority of the sample strongly agreed to experiencing
volatility, uncertainty, complexity, and ambiguity during the federal emergency period of
COVID-19. The values in Table 11 indicate that the sample for VUCA is not normally distributed
and is left skewed. The sample is leptokurtic in volatility, uncertainty, complexity, and ambiguity.
The mode across all VUCA variables is 6 (strongly agree). The median for volatility is 5
(moderately agree), and the median for uncertainty, complexity, and ambiguity is 6 (strongly
agree).

Table 10
Frequency Distributions: VUCA (N =171)
Response
Volatility Uncertainty Complexity Ambiguity
n % n % n % n %
Strongly disagree 7 4.1 5 2.9 6 3.5 6 3.5
Moderately disagree 3 1.8 3 1.8 2 1.2 1 0.6
Mildly disagree 5 2.9 3 1.8 3 1.8 3 1.8
Mildly agree 31 18.1 18 10.5 20 11.7 18 10.5
Moderately agree 49 28.7 43 25.1 40 23.4 38 22.2
Strongly agree 76 44.4 99 57.9 100 58.5 105 61.4
Table 11
Measures of Central Tendency: VUCA (N = 171)
Measure Volatility Uncertainty Complexity Ambiguity
Median 5 6 6 6
Mode 6 6 6 6
Range 5 5 5 5
Skewness –1.565 –2.082 –2.077 –2.238
Kurtosis 2.417 4.546 4.476 5.329
A Spearman’s rho was conducted to examine the correlation coefficients of VUCA. The
results in Table 12 indicate significant positive correlations between VUCA variables. Moderate
degrees of correlation occur amongst all correlations of VUCA, rs(169) = .543–.678, p < .001.
The strongest moderate degrees of correlation exist between volatility and complexity, followed
by complexity and uncertainty. The results of the correlations indicated that uncertainty
explained 43.0% of the variance of volatility (R2 = .430), complexity explained 46.0% of the

variance of volatility (R2 = .460), and ambiguity explained 23% of the variance of volatility (R2 =
.295).

80
Table 12
Correlation Coefficients: VUCA
Volatility Uncertainty Complexity Ambiguity
Spearman’s rho Volatility 1.000 .655** .678** .543**
Sig. (two-tailed) – p < .001 p < .001 p < .001
R squared – .429 .460 .295
N 171 171 171 171
Uncertainty .655** 1.000 .656** .556**
Sig. (two-tailed) p < .001 – p < .001 p < .001
R squared .429 – .430 .309
N 171 171 171 171
Complexity .678** .656** 1.000 .548**
Sig. (two-tailed) p < .001 p < .001 – p < .001
R squared .460 .430 – .300
N 171 171 171 171
Ambiguity .543** .556** .548** 1.000
Sig. (two-tailed) p < .001 p < .001 p < .001 –

R squared .295 .309 .300 –
N 171 171 171 171
**Correlation is significant at the 0.01 level (two-tailed).

81
A combined VUCA variable was computed from the total sum score from the ordinal
response variables of volatility, uncertainty, complexity, and ambiguity. The combined VUCA
variable values ranged from 4 to 24, with skewness of –2.28 and kurtosis of 6.03. The results in
Table 13 display the measures of central tendency of the combined VUCA variable.
Table 13
Measures of Central Tendency: Combined VUCA Variable (N = 171)
Measure Value
Mean 20.83
Median 22.00
Mode 24.00
Range 20.00
Std. deviation 4.24
A two-tailed Spearman’s rho was conducted to examine the relationship between the
combined VUCA variable and secondary traumatic stress, professional quality of life (positive
and negative), and task creativity. There was a significant weak positive linear correlation
between VUCA and secondary traumatic stress, rs(169) = .388, p < .001. The R/rho squared was
.15, reflecting the proportion of variance accounted for in secondary traumatic stress that is
predictable from VUCA. There was a nonsignificant correlation of rs(169) = .022, p = .777
between VUCA and positive professional quality of life. VUCA and negative professional
quality of life were significantly correlated, rs(169) = .309, p < .001. The R/rho squared was .10,
reflecting the proportion of variance accounted for in negative professional quality of life that is
82
predictable from VUCA. There was a nonsignificant correlation of rs(169) = .309, p = .368
between VUCA and task creativity.
The following tables display the descriptive results of the criterion variables of
professional quality of life, secondary traumatic stress, and creative activities during the federal
emergency period of COVID-19, including frequency counts and percentages and measures of
central tendency and dispersion. The results in Table 14 depict the frequency distributions of
professional quality of life, secondary traumatic stress, and engagement in task creativity. The
results in Table 15 indicate that the majority of participants occasionally experienced positive
professional quality of life, secondary traumatic stress, and task creativity, and frequently
experienced negative professional quality of life. The data are not normally distributed.
Table 14
Frequency Distributions: Professional Quality of Life (Positive & Negative), Secondary
Traumatic Stress, and Task Creativity (N = 171)
Response
PQL pos. PQL neg. STS Task creativity
n % n % n % n %
Never 16 9.4 4 2.3 19 11.1 5 2.9
Rarely 33 19.3 18 10.5 43 25.1 27 15.8
Occasionally 61 35.7 56 32.7 61 35.7 49 28.7
Frequently 52 30.4 60 35.1 35 20.5 49 28.7
Very frequently 9 5.3 33 19.3 13 7.6 41 24.0
Table 15
Measures of Central Tendency: Professional Quality of Life (Positive & Negative), Secondary
Traumatic Stress, and Task Creativity (N = 171)

83
Measure PQL pos. PQL neg. STS Task creativity
Median 3 4 3 4
Mode 3 4 3 3 a
Range 4 4 4 4
Skewness –.279 –.329 .071 –.272
Kurtosis –.527 –.338 –.588 –.802
a Multiple modes exist. The smallest value is shown.
A Spearman’s rho was conducted to examine the correlation coefficients of professional
quality of life (positive and negative), secondary traumatic stress, and task creativity. A
significant two-tailed negative moderate correlation exists between positive professional quality
of life and negative professional quality of life, rs(169) = –.499, p < .001. A significant twotailed
weak negative correlation exists between positive professional quality of life and secondary
traumatic stress, rs(169) = –.266, p = .003. A significant two-tailed positive moderate correlation
exists between negative professional quality of life and secondary traumatic stress, rs(169)
= .486, p < .001. A nonsignificant two-tailed correlation exists between task creativity and
positive professional quality of life, rs(169) = .116, p = .135; between task creativity and
negative professional quality of life, rs(169) = –.111, p = .147; and between task creativity and
secondary traumatic stress, rs(169) = –.088, p = .255. The R/rho squared reflects the proportion
of variance accounted for in the dependent variable that is predictable from the independent
variables. The results of the correlations indicated that negative professional quality of life
explained 24.9% of the variance in positive professional quality of life (R2 = .249); secondary
traumatic stress explained 5.1% of the variance in positive professional quality of life (R2
= .051); secondary traumatic stress explained 23.6% of the variance in negative professional

84
quality of life (R2 = .236); positive professional quality of life explained 24.9% of the variance in
negative professional quality of life (R2 = .249); negative professional quality of life explained
23.6% of the variance in secondary traumatic stress (R2 = .236); and positive professional quality
of life explained 5.1% of the variance in secondary traumatic stress (R2 = .051).
Variables Pertaining to Postpandemic Experience
The RDCA was administered to measure creativity in mental health providers following
the conclusion of the federal emergency period of the COVID-19 pandemic. The RDCA total
values ranged from 99–224, with skewness of –.89 and kurtosis of 1.74. The results in Table 16
display the measures of central tendency for the total sum score of the RDCA.
Table 16
Measures of Central Tendency: RDCA Total (N = 171)
Measure Value
Mean 181.84
Median 184.00
Mode 184.00
Range 125.00
Std. deviation 22.04
The CD-RISC-25 was administered to measure resilience in mental health providers
following the conclusion of the federal emergency period of the COVID-19 pandemic. The CD-
RISC-25 total values ranged from 38–95, with skewness of –.56 and kurtosis of .33. The results
in Table 17 display the measures of central tendency for the total sum score of the CD-RISC-25.

85
Table 17
Measures of Central Tendency: CD-RISC-25 Total (N = 171)
Measure Value
Mean 74.66
Median 75.00
Mode 70.00
Range 57.00
Std. deviation 11.80
Hypothesis Testing
Research Question 1
Research question 1, H10, and H1a pertained to the relationship between creativity and
resilience in mental health providers who experienced VUCA during the federal public health
emergency period of the COVID-19 pandemic. Correlational and regression analyses were used
to examine the extent to which the predictor variable, the RDCA, was predictive of the criterion
variable, the CD-RISC-25. The overall summed score of the CD-RISC-25 and the RDCA were
treated as continuous scale data and z scores were calculated. Assumptions were met for
normality, linearity, and homoscedasticity using histogram, p-p plot, and scatterplot. The kurtosis
of RDCA total was found to be 1.74, indicating that the distribution is platykurtic, producing
fewer and less extreme outliers than the normal distribution. The skewness of RDCA total was
found to be –.89, indicating that the distribution was left-skewed. The kurtosis of CD-RISC-25
total was found to be .33, indicating that the distribution is platykurtic, producing fewer and less
extreme outliers than the normal distribution. The skewness of CD-RISC-25 total was –.56
indicating that the distribution was left-skewed. The values for asymmetry and kurtosis between

86
–1.96 and +1.96 in a sample size less than 200 are considered acceptable in order to prove
normal univariate distribution. Because assumptions were met for parametric correlation, and
hypothesis 1 pertained to the relationship between one total score predictor variable and one total
score criterion variable, the study included a bivariate correlational analysis using the Pearson
product-moment correlation. Results of the Pearson product-moment correlation indicates a
significant strong positive linear relationship between the overall scores of the RDCA and the
CD-RISC-25, r(169) =.715, p < .001.
To investigate the predictive relationship between creativity and resilience in mental
health providers, a simple linear regression was conducted. The predictor was the total score of
the RDCA and the outcome was the total score of the CD-RISC-25. The predictor variable was
statistically significant, B = .383, 95% CI [.326, .440], p < .05, indicating that for every one unit
increase in the RDCA, the CD-RISC-25 changed by +.383 units. The model explained
approximately 51% of the variability, R2 = .511. Therefore, H10 is rejected, and the alternative
hypothesis, H1a, is retained.
To examine further how VUCA affected mental health providers during COVID, a
moderation regression analysis was performed to determine the extent to which VUCA
moderated the relationship between creativity and resilience. The criterion variable for the
analysis was resilience, as measured by the total score of the CD-RISC-25. The predictor
variable was creativity, as measured by the total score of the RDCA. The moderator variable was
VUCA, as measured by the sum score of VUCA variables. The regression revealed a significant
strong positive relationship between creativity and resilience, B = .721, 95% CI, p <.05. The
relationship between VUCA and resilience was not statistically significant, B = –.087, 95% CI, p
= .110]. The moderation effect of VUCA on the relationship between creativity and resilience

87
was not significant B = –.371, 95% CI, p = .511]. The results indicate that VUCA did not
moderate the relationship between creativity and resilience. A Spearman’s rho was used to
examine the relationship between the combined VUCA variable and the total score of the RDCA.
A significant weak positive linear relationship exists, rs(169) = .178, p = .020.
Research Question 2
Research question 2, H20, and H2a pertained to the relationship between task creativity
and resilience in mental health care providers who engaged in creative activities during the
federal public health emergency period of the COVID-19 pandemic. In the current study, I used a
correlational and regression analysis to examine the extent to which the predictor variable,
creative tasks, was predictive of the criterion variable, resilience,as measured by the overall score
of the CD-RISC-25. Because hypothesis 2 is concerned with the relationship between one
ordinal predictor variable and one scaled criterion variable, the study included a bivariate
correlational analysis using the nonparametric Spearman’s rho. The results indicate a significant
weak positive linear correlation, rs(169) = .291, p < .05, between creative tasks and the total
score of the CD-RISC-25.
Assumption testing was conducted for regression analysis to examine the residuals to
check for linearity, normality, independence, and homoscedasticity. Assumptions were met for
linearity, normality, and independence, but the residuals yielded heteroscedasticity; therefore, a
weighted least squares regression was conducted to correct and reestimate the model to
determine if creative tasks significantly predicted resilience. The results indicated that the
predictor, creative tasks, explained 8.1% of the variance, R2 = .08, F(14.84), p < .0001. Creative
tasks significantly predicted resilience, B = 3.168, p < .001, indicating that for every one unit

88
increase in creative tasks, the CD-RISC-25 increased by +3.17 units. Therefore, H20 is rejected,
and the alternative hypothesis, H2a, is retained.
Research Question 3
Research question 3, H30, and H3a pertained to the relationship between professional
quality of life and resilience in mental health care providers who experienced VUCA during the
federal public health emergency period of the COVID-19 pandemic. A correlational and
regression analysis was used to examine the extent to which professional quality of life (positive
and negative) was predictive of resilience, as measured by the overall score of the CD-RISC-25.
Hypotheses 30 and 3a concerned the relationship between one ordinal predictor variable and one
scaled criterion variable; therefore, a bivariate correlational analysis using the nonparametric
Spearman’s rho was conducted. The results indicate an insignificant relationship, rs(169) =
– .144, p = .06, between negative professional quality of life and resilience. Given the
nonsignificant correlation, I did not conduct regression analysis for this relationship.
The results indicate a significant weak positive correlational relationship, rs(169) = .233,
p = .002, between positive professional quality of life and resilience. I used regression analysis to
examine this relationship. Assumption testing was conducted for regression analysis to examine
the residuals of positive professional quality of life to check for linearity, normality,
independence, and homoscedasticity. Assumptions were met for linearity, normality, and
independence, but the residuals yielded heteroscedasticity; therefore, a weighted least squares
regression was conducted to correct and reestimate the model to determine if positive
professional quality of life significantly predicted resilience. The results included in Tables 18,
19, and 20 indicated there was insufficient evidence in the sample to conclude that a nonzero
correlation exists, as the p value is greater than .05. However, evidence exists of a significant

89
positive correlational relationship between positive professional quality of life and resilience,
rs(169) = .233, p = .002. Therefore, the alternative hypothesis, H3a, is partially retained for the
relationship between positive quality of life and resilience but rejected for negative professional
quality of life and resilience.
90
Table
18
Model Summary Weighted Least Squares Regression: Positive Professional Quality of Life with
CD-RISC-25 Total Score
Model
Multiple
R
R
square
Adjusted R
square
Std. error of the
estimate
1 .099 .010 .004 8.953
Note. Predictors: (Constant), positive professional quality of life. Criterion variable: CD-RISC
total.
Table 19
ANOVA: Positive Professional Quality of Life with CD-RISC-25 Total Score
Measure Sum of squares df MS F Sig.
Regression 133.190 1 133.190 1.662 .199
Residual 13546.541 169 80.157
Total 13679.731 170
Table 20
Coefficients
Unstandardized Standardized
Measure coefficients coefficients
b Std. error β Std. error t Sig.
(Constant) 71.606 2.404 29.791 p < .001
PQLPos 1.032 .800 .099 .077 1.289 .199

91
Research Question 4
Research question 4, H40, and H4a pertained to the extent that secondary traumatic stress
moderated the relationship between creativity and resilience in mental health care providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic. A moderation analysis was conducted to determine the extent to which secondary
traumatic stress moderated the relationship between creativity and resilience in mental health
care providers. The criterion variable for the analysis was resilience, as measured by the total
score of the CD-RISC-25. The predictor variable was creativity, as measured by the total score of
the RDCA. The moderator variable was secondary traumatic stress. The results displayed in
Tables 21–25 indicate a significant relationship between creativity and resilience, B = .714, 95%
CI, p < .05. The relationship between secondary traumatic stress and resilience was statistically
significant B = –.208, 95% CI, p < .05. The moderation effect of secondary traumatic stress on
the relationship between creativity and resilience was not significant, B = .039, 95% CI, p
= .491]. The results identify that secondary traumatic stress did not moderate the relationship
between creativity and resilience, thus retaining the null hypothesis H40.
21
Model Summary of Linear Regression: RDCA Total with CD-RISC-25 Total Moderated by
Secondary Traumatic Stress
Model R
R
square
Adjusted R
square
Std. error of the
estimate
1 .745 a .555 .547 .67337801
Note. Criterion variable: z score: CD-RISC total.

92
Table
a Predictors: (Constant), INT_STS_RDCA, z score: STS, z score: RDCA total.
Table 22
ANOVA: RDCA Total with CD-RISC-25 Total Moderated by Secondary Traumatic Stress
Model
Sum of
squares df MS F Sig.
1
Regression
94.276
3
31.425
69.304
p < .001 a
Residual 75.724 167 .453
Total 170.000 170
Note. Criterion variable: z score: CD-RISC total.
a Predictors: (Constant), INT_STS_RDCA, z score: STS, z score: RDCA total.
93
Table
23
Coefficients: RDCA Total with CD-RISC-25 Total Moderated by Secondary Traumatic Stress
Unstandardized Standardized Collinearity coefficients coefficients
statistics
Model b Std. error β t Sig. Tolerance VIF
1
(Constant)
.000
.051
–.008
.994
z score: RDCA
total
.714 .052 .714 13.751 p < .001 .990 1.010
z score: STS –.208 .052 –.208 –4.007 p < .001 .992 1.008
INT_STS_RD
CA
.039 .057 .036 .690 .491 .982 1.018
Note. Criterion variable: z score: CD-RISC total.
Table 24
Collinearity Diagnostics: RDCA Total with CD-RISC-25 Total Moderated by Secondary
Traumatic Stress
Model Dimension Eigenvalue
Variance proportions
Condition index
(Constant)
z score:
RDCA total
z score:
STS
INT_STS
_RDCA
1 1 1.140 1.000 .00 .24 .20 .41
2 1.000 1.068 .99 .00 .00 .00
3 0.990 1.073 .00 .45 .55 .00
4 0.870 1.144 .00 .30 .24 .59
Note. Criterion variable: z score: CD-RISC total.

94
Table
25
Residuals Statistics: RDCA Total with CD-RISC-25 Total Moderated by Secondary Traumatic
Stress (N = 171)
Measure Minimum Maximum Mean SD
Predicted value –2.9772470 1.5056908 .0000000 .74469048
Residual –2.09208965 1.80718648 .00000000 .66740999
Std. predicted value –3.998 2.022 .000 1.000
Std. residual –3.107 2.684 .000 .991
Note. Criterion variable: z score: CD-RISC total.
Research Question 5
Research question 5 pertains to the predictive relationship between individual factors of
creativity and resilience. A factor analysis is necessary to answer this question pertaining to the
40 individual factors of the RDCA and the 25 individual factors of the CD-RISC-25. A sufficient
sample size was not attained in the current study to perform hypothesis testing for RQ5.
Research Question 6
Research question 6 pertained to the relationship of subfactors of creativity to resilience
and was examined using correlational and weighted multiple regression analyses. Assumption
testing was conducted to examine the residuals to check for linearity, normality, independence,
and homoscedasticity. The subscale scores of the RDCA did not meet assumptions for parametric
analysis; therefore, the nonparametric Spearman’s rho was used. The 11 subscale scores of the
RDCA and the total summed score of the CD-RISC-25 were analyzed using a Spearman’s rho to
determine correlation coefficients. The results indicated a significant strong positive correlational
relationship between intrinsic motivation and resilience, rs(169) = .614, R2 = .377, p < .001. A

95
moderate positive correlational relationship was evident between risk taking and resilience,
rs(169) = .569, R2 = .324, p < .001; flexibility and resilience, rs(169) = .563, R2 = .317, p < .001;
tolerance of ambiguity and resilience, rs(169) = .543, R2 = .295, p < .001; divergent thinking and
resilience, rs(169) = .495, R2 = .245, p < .001; originality and resilience, rs(169) = .487, R2 = .237,
p < .001; fluency and resilience, rs(169) = .479, R2 = .229, p < .001; resistance to premature
closing and resilience, rs(169) = .431, R2 = .186, p < .001; and convergent thinking and
resilience, rs(169) = .401, R2 = .161, p < .001. A significant weak positive correlation was evident
between elaboration and resilience, rs(169) = .276, R2 = .076, p < .001. There was no significant
correlation between extrinsic motivation and resilience. The results identify there are 10 subscale
factors of creativity that have significant correlations with resilience. The results support
rejecting the null hypothesis, H60, and retaining the alternative hypothesis, H6a.
Assumption testing was conducted for regression analysis to examine the residuals to
check for linearity, normality, independence, and homoscedasticity. Assumptions were met for
linearity, normality, and independence, but the residuals yielded heteroscedasticity; therefore, a
weighted least squares regression was conducted to correct and reestimate the model to
determine if the subfactors of creativity significantly predicted resilience. A weighted multiple
regression was run to predict resilience from originality, fluency, flexibility, elaboration, intrinsic
motivation, extrinsic motivation, resistance to premature closure, tolerance of ambiguity,
divergent thinking, convergent thinking, and risk-taking. The model indicated a strong level of
prediction, R = .754. The results indicated the predictors explained 56.9% of the variance, R2
= .569, F(19.07), p < .001. Creativity subfactors significantly predicted resilience, F(11,159) =
19.067, p < .001, indicating that the regression model is a good fit of the data. The coefficients
are reported in Table 26. Flexibility, intrinsic motivation, and risk-taking significantly predicted

96
True nearly all
the time
(4)
resilience (p < .05). The results support rejecting the null hypothesis, H60, and retaining the
alternative hypothesis, H6a.
Table 26
Coefficients: RDCA Subfactors
Unstandardized Standardized coefficients
coefficients
Measure b Std. error β Std. error t Sig.
(Constant) –3.121 6.537 –0.478 .634
Originality –0.111 0.198 –.052 .093 –0.562 .575
Fluency –0.229 0.392 –.063 .107 –0.583 .560
Flexibility 1.015 0.463 .204 .093 2.191 .030*
Elaboration 0.051 0.229 .016 .072 0.225 .823
Intrinsic motivation 1.435 0.339 .321 .076 4.234 .000*
Extrinsic motivation 0.060 0.208 .016 .055 0.290 .772
Resistance to premature
closure
0.294 0.286 .068 .066 1.026 .306
Tolerance of ambiguity 0.314 0.409 .058 .076 0.766 .445
Divergent thinking 0.496 0.356 .102 .073 1.392 .166
Convergent thinking 0.508 0.291 .109 .062 1.748 .082
Risk taking 0.981 0.322 .244 .080 3.044 .003*
*Correlation is significant at the 0.05 level.

Summary
The contents of Chapter 4 included a review of data collection, including recruitment,
data analysis, the characteristics of the sample, and the results. Study variables pertaining to
experiences during the COVID-19 federal emergency period included VUCA, professional
quality of life (positive and negative), secondary traumatic stress, and task creativity and were
analyzed using descriptive and inferential statistics. The analysis of the results of the RDCA and
the CD-RISC-25 reflecting creativity and resilience during the postpandemic period included
measures of central tendency. Hypotheses testing included correlational (Pearson productmoment
and Spearman’s rho) and regression analyses.
The research questions focused on the examination of various relationships among the
aforementioned variables in mental health providers who experienced VUCA during the federal
public health emergency period of the COVID-19 pandemic. For the first research question, a
Pearson product-moment correlation coefficient test indicated a significant positive linear
relationship between creativity and resilience. In a regression analysis, creativity was significant
in predicting resilience. A moderation regression analysis indicated a significant relationship
between creativity and resilience but the relationship between VUCA and resilience was not
statistically significant. I rejected the null hypothesis, H10, and retained the alternative
hypothesis, H1a. For the second research question, a Spearman’s rho indicated a weak positive
linear correlation between creative tasks and resilience, and a weighted least squares regression
indicated that creative tasks significantly predicted resilience. I rejected the null hypothesis, H20,
and retained the alternative hypothesis, H2a. For the third research question, a Spearman’s rho
revealed a significant weak positive correlational relationship between positive professional
quality of life and resilience and an insignificant correlational relationship between negative

98
True nearly all
the time
professional quality of life and resilience. A weighted least squares regression indicated
insufficient evidence to determine the predictive relationship between positive professional
quality of life and resilience. However, there was evidence of a significant positive correlational
relationship between positive professional quality of life and resilience, rs(169) = .233, p = .002.
Therefore, the alternative hypothesis, H3a, was partially retained for the relationship between
positive quality of life and resilience and rejected for negative professional quality of life and
resilience. For the fourth research question, moderation regression analysis indicated a
significant relationship between creativity and resilience and between secondary traumatic stress
and resilience. Secondary traumatic stress did not moderate the relationship between creativity
and resilience, thus leading to retaining the null hypothesis H40. I did not conduct hypothesis
testing for the fifth research question due to an insufficient sample size to perform a factor
analysis. For the sixth research question, a Spearman’s rho indicated a significant strong positive
correlational relationship between intrinsic motivation and resilience. A moderate positive
correlational relationship was evident between risk-taking, flexibility, tolerance of ambiguity,
divergent thinking, originality, fluency resistance to premature closing, and convergent thinking.
A significant weak positive correlation was evident between elaboration and resilience. No
significant correlation existed between extrinsic motivation and resilience. A weighted least
squares regression indicated that flexibility, intrinsic motivation, and risk-taking significantly
predicted resilience. The results support rejecting the null hypothesis, H60, and retaining the
alternative hypothesis, H6a.

Chapter 5 includes the interpretation and discussion of the results and conclusions drawn
from the findings in terms of where they confirm, disconfirm, or extend theory and the body of
scholarly literature. The limitations of the study will be reviewed in terms of generalizability,
validity, and reliability that arose from the execution of the study. Recommendations for future
research will be discussed. The implications of the findings for promoting resilience in mental
health providers through creativity to mitigate secondary traumatic stress are also included in
Chapter 5.

100
True nearly all
the time
CHAPTER 5: DISCUSSION
The purpose of this quantitative predictive correlational study was to examine the
predictive relationship between creativity and resilience in mental health providers who
experienced VUCA while working in the United States during the federal public health
emergency period of the COVID-19 pandemic, which began on January 31, 2020, and ended on
May 11, 2023 (Silk et al., 2023). Adapting and navigating volatile, uncertain, complex, and
ambiguous (VUCA) environments, such as the COVID-19 pandemic, is necessary to generate
resiliency within the self and the collective system. In VUCA environments, creativity and
innovation are critical when new and complex issues arise (Mumford & Todd, 2019), fostering
flexibility, presence, problem-solving, and risk-taking (Arnout & Almoied, 2020; Cropley, 2020;
Reisman et al., 2016). Identifying factors of creativity that contribute to resiliency can mitigate
secondary traumatic stress symptoms in mental health providers.
The study included six research questions and six hypothesis pairs, with five null
hypotheses tested. The first question pertained to the relationship between creativity (predictor
variable) and resilience (criterion variable) in mental health providers. The second question
pertained to the relationship between task creativity (predictor variable) and resilience (criterion
variable). The third question pertained to the relationship between professional quality of life
(predictor variable) and resilience (criterion variable). The fourth question pertained to the extent
to which secondary traumatic stress (moderating variable) moderated the relationship between
creativity (predictor variable) and resilience (criterion variable). The fifth question pertained to

which factors of creativity (predictor variable) predict resilience (criterion variable). The sixth
question pertained to which subfactors of creativity (predictor variable) predict resilience
(criterion variable).
Chapter 5 begins with a review of the major findings. The interpretation and discussion of
the results will follow with conclusions drawn from the findings in terms of where they confirm,
disconfirm, or extend theory. The chapter continues with a discussion of the implications of the
findings for research and practice, limitations, recommendations, and suggestions for future
research. The chapter concludes with a final summary.
Findings
This section includes a summary of the major findings of the study, beginning with the
characteristics of the sample and variables pertaining to experiences during the COVID-19
federal emergency period, including VUCA, professional quality of life (positive and negative),
secondary traumatic stress, and task creativity. The next section includes a summary of the
findings pertaining to the postpandemic period reflecting creativity and resilience. The final
section pertains to answers to the research questions. The summary of results serves as a
foundation for interpretations and conclusions about the findings in the next section.
Characteristics of the Sample
The current study yielded 171 participants ages 40–54 with more than 16 years of
experience in the field. Most were White or Latina women. Most of the sample were licensed
MA/MSW-level counselors/therapists and licensed doctoral-level psychotherapists. Clinicians,
clinical supervisors, and creative arts therapists represented the largest groups of the sample.
Private practice and community mental health centers were their primary workplaces. The
majority of the sample were not members of the NCTSN.

102
True nearly all
the time
Findings Pertaining to Experiences During COVID-19 Federal Emergency Period
A vast majority of the sample agreed that they experienced COVID-19 as a VUCA
environment, reporting volatility, uncertainty, and ambiguity. The mean score for the combined
VUCA variable indicated strong agreement to experiencing VUCA during the pandemic. A
majority occasionally experienced positive professional quality of life, secondary traumatic
stress, and task creativity and frequently experienced negative professional quality of life.
VUCA had a significant weak positive relationship with negative professional quality of
life and with secondary traumatic stress. No significant relationships were found between VUCA
and positive professional quality of life or VUCA and task creativity. Hypothesis testing revealed
a significant negative moderate relationship between positive professional quality of life and
negative professional quality of life. No significant relationships were found between task
creativity and positive professional quality of life, task creativity and negative professional
quality of life, or task creativity and secondary traumatic stress.
Findings Pertaining to Postpandemic Experience
The RDCA, measuring creativity in mental health providers, indicated moderately high
creativity in the sample during the postpandemic period. The CD-RISC-25 measured resilience,
and the total score for the sample was 74.66, less than five points below the mean score of the
U.S. general population.
Answers to Research Questions
The research questions focused on various relationships between the aforementioned
variables in mental health providers who experienced VUCA during the federal public health

emergency period of the COVID-19 pandemic. A brief summary of the findings follows. No
findings were obtained for the fifth research question due to an insufficient sample size to
support factor analysis.
Research Question 1
The findings indicated a significant strong positive linear relationship between creativity
and resilience. Creativity was a significant predictor of resilience. While the findings indicated a
significant relationship between creativity and resilience, the relationship between VUCA and
resilience was not significant. The findings revealed a significant weak positive linear
relationship between the combined VUCA variable and the total score of the RDCA.
Research Question 2
The findings revealed a significant weak positive linear relationship between creative
tasks and resilience. Creative tasks were predictive of resilience.
Research Question 3
The findings revealed a significant weak positive relationship between positive
professional quality of life and resilience. The relationship between negative professional quality
of life and resilience was not significant. There was insufficient evidence to conclude a
significant predictive relationship between positive professional quality of life and resilience.
Research Question 4
The findings indicated a significant strong positive relationship between creativity and
resilience and a weak negative relationship between secondary traumatic stress and resilience.
Secondary traumatic stress did not moderate the relationship between creativity and resilience.

104
True nearly all
the time
Research Question 6
The findings indicated a significant strong positive relationship between intrinsic
motivation and resilience. The results also revealed significant moderate positive relationships
between eight subfactors of creativity and resilience, including risk-taking, flexibility, tolerance
of ambiguity, divergent thinking, originality, fluency resistance to premature closing, and
convergent thinking. A significant weak positive correlation was evident between elaboration and
resilience. Flexibility, intrinsic motivation, and risk-taking significantly predicted resilience.
No significant relationship was found between extrinsic motivation and resilience.
Conclusions
This section includes the interpretation and discussion of the results and conclusions
drawn from the findings in terms of where they confirm, disconfirm, or extend theory and the
body of scholarly literature. The section begins with the characteristics of the sample, variables
pertaining to experiences during the COVID-19 federal emergency period, and variables
pertaining to experiences during the postpandemic period. The final section addresses the
conclusions for each component of the research questions and a discussion of the findings.
Characteristics of the Sample
In the current study, the sample consisted of mental health practitioners working in the
United States during the COVID-19 federal emergency period. The majority were White female
clinicians with multiple roles providing direct client services in private practice and community
mental health centers. The sample is representative of the U.S.-based mental health provider
community, which is mostly composed of White women (National Alliance on Mental Illness,

2022). I could not compare the sample to nationwide demographics of practitioners, nor to the
population of the NCTSN, because I did not have access to those data. The focus of the current
study on mental health providers addresses a gap in the literature where prior studies focused on
leaders in industry and medicine (Alkhaldi et al., 2017a; Anser et al., 2022; Baskin & Bartlett,
2021; Brendel et al., 2016; Krauter, 2019). Despite the importance of leaders’ perspectives, there
is a lack of published studies focused on direct service mental health providers. In the current
study, participants held various positions of direct and indirect service in mental health,
reflecting a more diverse sample than earlier studies that focused solely on social workers (Dima
et al., 2021) or counselors (Litam et al., 2021; Sklar et al., 2021). Creative art therapists
represented more than 14% of the population, which may affect the results of creativity scores in
the current study, as creative practices and mindsets are inherent in this population. I could not
make comparisons of creative art therapists to the total national population of behavioral health
practitioners as I did not have access to those data.
Through the focus on U.S. mental health providers who worked during COVID-19, the
findings of the current study further contribute to the literature on providers’ experiences during
the pandemic and postpandemic. The study extends the research on this population beyond
earlier studies that focused on providers’ experiences during the early stages of the pandemic
(Dima et al., 2021; Litam et al., 2021). Prior research focused on international populations
(Abdolkarimi et al., 2022; Dima et al., 2021; Krauter, 2019; Leask & Ruggunan, 2021), which
may differ from the experiences of U.S.-based participants.
Findings Pertaining to Experiences During COVID-19 Federal Emergency Period
Mental health providers experienced the pandemic as a VUCA environment regarding
volatility, uncertainty, complexity, and ambiguity. The current study results support and extend

106
True nearly all
the time
prior theoretical research identifying the COVID-19 pandemic as a volatile, uncertain, complex,
and ambiguous (VUCA) environment that created unpredictability and strain on health care
providers (Baskin & Bartlett, 2021; Fish & Mittal, 2021; Sklar et al., 2021).
Despite the theoretical connection to VUCA reported in prior studies (Baskin & Bartlett,
2021; Fish & Mittal, 2021; Sklar et al., 2021), published literature on VUCA environments is
scarce, and there is a dearth of research conducted on how the COVID-19 pandemic qualified as
a VUCA environment. Prior studies have focused on leaders within organizational systems and in
health care with assumed experiences of VUCA generalized from experiences of adverse
conditions and complex environments (Alkhaldi et al., 2017a, 2017b; Brendel et al., 2016;
Krauter, 2019).
Prior to this study, there were no published methods to measure VUCA during the
COVID-19 pandemic. In the current study, VUCA was measured using individualized variables
for volatility, uncertainty, complexity, and ambiguity, allowing for specific independent analysis
of each component. The combined VUCA variable represented the summed responses from each
participant, indicating a cumulative experience of volatility, uncertainty, complexity, and
ambiguity. The results of the current study provided evidence of COVID-19 as a VUCA
environment. Furthermore, the study results have practical applications for identifying VUCA in
environments. The VUCA variables created for this study contribute to the field and provide a
methodological basis for future investigation that could enable organizations to identify,
understand, navigate, and leverage the complexities inherent in VUCA environments.

In the current study, the majority of participants occasionally experienced positive
professional quality of life and secondary traumatic stress and frequently experienced negative
professional quality of life during the COVID-19 federal emergency period. These results
supported earlier findings that social workers experienced high perceived stress and burnout
levels during COVID-19 (Dima et al., 2021). The current study results revealed a significant
negative moderate relationship between positive professional quality of life and negative
professional quality of life. Positive professional quality of life refers to the positive effects of
work-related stressors on helpers, such as compassion satisfaction, a sense of purpose, increased
productivity, mattering, contributing to the greater good in the lives of clients, and fulfilling the
human needs for self-efficacy, self-determination, and belonging. Negative professional quality
of life refers to work-related stressors on helpers, such as compassion fatigue, secondary
traumatic stress, burnout, institutional betrayal, and moral injury. The study results indicated a
significant negative weak relationship between positive professional quality of life and secondary
traumatic stress. Enhancing providers’ positive professional quality of life can mitigate
compassion fatigue, secondary traumatic stress, and burnout. Additionally, the results revealed a
significant positive moderate relationship between negative professional quality of life and
secondary traumatic stress.
The results of the current study determined that mental health providers experienced
COVID-19 as a VUCA environment. The results of the study confirm earlier studies by
demonstrating that mental health providers can experience a positive professional quality of life
during VUCA environments such as COVID-19 (Epstein et al., 2020; Fish & Mittal, 2021).
Positive professional quality of life is evident in the sample during COVID-19, but no significant
predictive relationship was found between VUCA and positive professional quality of life. The

108
True nearly all
the time
relationship between VUCA and negative professional quality of life was significant, positive,
and weak, suggesting that mental health providers who experienced VUCA were likely to have
experienced negative effects of work-related stressors, such as compassion fatigue, burnout,
institutional betrayal, and moral injury, including symptoms of fatigue, skepticism, and decreased
personal and professional efficacy. Prior to the pandemic, mental health providers were
disproportionately vulnerable to compassion fatigue, secondary traumatic stress, and burnout
(Miller et al., 2016; Morse et al., 2012; Rudaz et al., 2017). In a study during the early stage of
COVID-19, secondary traumatic stress (STS) symptoms and burnout were increasing in
providers who had already been experiencing job-related stressors prior to the pandemic (Vîrgă
et al., 2020). In the current study, the relationship between VUCA and secondary traumatic stress
was significant, positive, and weak, indicating that mental health providers who experienced
VUCA were likely to have also experienced secondary traumatic stress.
In the current study, the results for task creativity were multimodal, with most of the
sample reporting occasional and frequent engagement in creative activities, such as personal
creation of art, music, dance, poetry, and crafts during COVID-19. The frequent engagement in
task creativity may reflect the sample, as more than a tenth of the sample were creative arts
therapists who often engaged in artmaking as part of their professional work and self-care. Task
creativity is evident in the sample during COVID-19, but there was no predictive relationship
found between VUCA and task creativity.
No significant relationships were found between task creativity and positive professional
quality of life, task creativity and negative professional quality of life, or task creativity and

secondary traumatic stress. The results may not have revealed significant relationships due to
temporal factors, such as the inability to capture long-term predictive relationships between task
creativity and professional quality of life or secondary traumatic stress. These relationships might
be delayed or emerge over an extended period of time.
Findings Pertaining to Postpandemic Experience
Mental health providers reported moderately high levels of creativity during the
immediate postpandemic period. The use of the RDCA as an instrument in the current study
extends the methodological application beyond earlier studies to include the RDCA (Reisman et
al., 2016) as a measure of creativity for mental health providers and in correlational investigation
with the CD-RISC-25 (Connor & Davidson, 2003).
Mental health providers demonstrated resilience in the postpandemic period. Resilience
was measured by the CD-RISC-25, and the total score for the sample represented the bottom
50% of the general population. Compared to physicians during a 2021 survey who scored in the
bottom 25% of the general population, mental health providers in the current study demonstrated
higher resilience postpandemic than physicians prior to the pandemic (Connor & Davidson,
2003; Nituica et al., 2021). Authors of prior studies defined resilience as the ability to adapt
positively to adverse or traumatic experiences (Baskin & Bartlett, 2021). The results from the
current study confirm these findings and indicate that mental health providers who experienced
VUCA during the pandemic displayed postpandemic resilience or positive adaptation to
stressors.
The CD-RISC-25 was widely used in prior studies with diverse populations in health
care, industry, education, and the military (Abdolkarimi et al., 2022; Baskin & Bartlett, 2021;

110
True nearly all
the time
Connor & Davidson, 2003). The current study addresses a gap in the published literature on
using the CD-RISC-25 with U.S.-based mental health providers during the pandemic.
Answers to Research Questions
Research Question 1
The null hypothesis tested for R1 pertained to the predictive relationship between
creativity (predictor variable) and resilience (criterion variable) in mental health providers who
experienced VUCA during the federal public health emergency period of the COVID-19
pandemic. Creativity strongly predicted resilience, and the model explained 51% of the
variability. Providers with higher creativity had greater resilience.
The results of the current study supported the conclusion that creativity predicted
resilience, identifying creativity as a contributing factor to resilience. Prior studies identified that
resiliency contributed to workplace creativity in nurses (Anwar et al., 2020) and psychological
counselors (Arnout & Almoied, 2020). The results from the current study confirmed the inverse
finding that creativity predicted resilience in mental health providers. Understanding the
relationship between creativity and resilience can have implications for personal development,
education, mental health interventions, and organizational practices. Fostering creativity may not
only enhance one’s ability to generate innovative ideas but may also contribute to building
resilience in the face of life’s challenges.
In the current study, mental health providers experienced high levels of VUCA during the
COVID-19 pandemic and moderately high creativity in the immediate postpandemic period. A
weak significant relationship exists between experiences of VUCA and postpandemic creativity,

indicating that mental health providers experienced VUCA and had moderately high creativity.
The study indicates that mental health providers who experienced VUCA during the pandemic
displayed postpandemic resilience, suggesting that experiencing VUCA during the pandemic
may have contributed to the resilience of mental health providers. Mental health providers may
have developed adaptability skills to navigate the challenging and unpredictable circumstances of
COVID-19. Adaptability is a key component of resilience, as it involves adjusting to new
situations and bouncing back from setbacks.
Further testing of the relationship between VUCA and resilience did not reveal significant
relationships. VUCA did not moderate the relationship between creativity and resilience. The
absence of significant relationships may have been due to interactions with other variables,
obscuring the relationship. Individual differences, such as personality traits, coping styles, or
prior experiences, may moderate the relationship between VUCA and resilience. The lack of
consideration or control of these factors may contribute to the absence of significant correlations.
Threshold effects may also be evident, where a significant relationship was not detected because
the critical point needed for observed correlation was not reached.
In prior studies, VUCA environments created adverse conditions that decreased leaders’
adaptive performance and creativity (Krauter, 2019). The results from the current study
disconfirmed the findings from Krauter (2019). VUCA environments correlated to moderately
high creativity in the postpandemic period, demonstrating that as VUCA increases, creativity
increases. Theorists postulated that VUCA environments require leaders to be resilient, tolerate
ambiguity (Brendel et al., 2016), become flexible, problem-solve, and engage in divergent
thinking (Alkhaldi et al., 2017a, 2017b). These qualities are mirrored within the creativity
paradigm as measured by the RDCA in the current study. The creativity of mental health

112
True nearly all
the time
providers predicted their resilience, implying that they were more adept at navigating and
adapting to changes, which is a critical aspect of resilience in dynamic environments.
The current study did not include comparisons of creativity during the pandemic with
creativity postpandemic. The postpandemic scores revealed moderately high creativity, reflecting
characteristics of personality that indicate trait-based creativity (Reisman et al., 2016). Traits
reflect longstanding, characteristic patterns of behavior, thought, and feeling (Schmitt & Blum,
2020). Based on the findings from the current study, trait-based creativity that was evident in the
postpandemic experience was likely present during the pandemic experience.
Research Question 2
The associated null and alternative hypotheses tested for R2 pertained to the predictive
relationship between task creativity and resilience in mental health care providers who engaged
in creative activities during the federal public health emergency period of the COVID-19
pandemic. The majority of mental health providers in the current study occasionally engaged in
task creativity during the pandemic. A weak positive linear relationship existed between task
creativity and resilience. Creative tasks significantly predicted resilience, indicating that the more
mental health practitioners engaged in creative tasks during the pandemic, the more resilient they
were during the postpandemic period.
The benefits of creative endeavors were investigated in prior studies and contributed to
positive emotion during pandemic-related social isolation (Elisondo, 2021; Kapoor & Kaufman,
2020). Richards (2007) discussed that in tasks of everyday life, creativity can serve as a method
to adapt to challenges. In the current study, task creativity predicted resilience, supporting the

conclusion that task creativity is a method to positively adapt to adverse or traumatic
experiences. Creative expression, whether through art, writing, or other outlets, provides
individuals with a constructive way to process emotions and cope with stress. The results of the
current study support that creative tasks are resiliency-building endeavors that could be fostered
as best practices to support mental health providers.
Research Question 3
The associated null and alternative hypotheses tested for R3 pertained to the predictive
relationship between professional quality of life and resilience in mental health care providers
who experienced VUCA during the federal public health emergency period of the COVID-19
pandemic. The relationship found between positive professional quality of life and resilience was
significant, positive, and weak. The current study revealed no significant relationships between
negative professional quality of life and resilience, and there was insufficient evidence to
determine the predictive relationship between positive professional quality of life and resilience.
The scales used to measure negative professional quality of life and resilience might not have
been aligned in terms of sensitivity, preventing the detection of subtle correlations.
Mental health providers experienced positive professional quality of life or positive
effects of work-related stressors, such as compassion satisfaction, a sense of purpose, increased
productivity, mattering, contributing to the greater good in the lives of clients, and fulfilling the
human needs for self-efficacy, self-determination, and belonging. In prior studies, positive
effects, or compassion satisfaction, were experienced in response to traumatic and stressful
events (Lluch-Sanz et al., 2022; Stamm, 2009). The results of the current study confirm prior
research and indicate an association exists between positive professional quality of life and
resilience in mental health providers who experienced VUCA during the pandemic. The

114
True nearly all
the time
experience of VUCA may have prompted mental health providers to develop and employ
effective coping strategies to manage their own well-being, support colleagues, and deliver care
to clients even in challenging circumstances.
Research Question 4
The associated null and alternative hypotheses tested for R4 pertained to what extent
secondary traumatic stress moderated the relationship between creativity and resilience in mental
health care providers who experienced VUCA during the federal public health emergency period
of the COVID-19 pandemic. Creativity significantly predicted resilience. Secondary traumatic
stress significantly and negatively predicted resilience, and secondary traumatic stress did not
moderate the relationship between creativity and resilience.
Exploration within prior studies has focused on resilience as a positive adaptation to
stressors and a predictor that mitigates the impact of compassion fatigue, secondary traumatic
stress, and burnout (Arnout & Almoied, 2020; Metzl & Morrell, 2008). In the current study, there
was a negative correlation between secondary traumatic stress and resilience. Secondary
traumatic stress did not moderate the relationship between creativity and resilience. This finding
further supports creativity as a predictor of resilience, even when providers have experienced
secondary traumatic stress. More creative individuals are better able to bounce back from
adversity or stress, even when they have experienced secondary traumatic stress. Kartsonaki et
al. (2023) found that secondary traumatic stress resulted in long-term symptoms of isolation and
exhaustion that impaired one’s quality of life. Despite the negative impact of secondary traumatic
stress on isolation, exhaustion, and quality of life, the findings of the current study support that

creative individuals still exhibit resilience. This resilience implies an ability to cope with and
overcome the challenges posed by secondary traumatic stress.
Research Question 5
Hypothesis testing was not conducted for R5 due to an insufficient sample size to perform
a factor analysis.
Research Question 6
The associated null and alternative hypotheses tested for R6 pertained to which subfactors
of creativity predict resilience in mental health care providers who experienced VUCA during the
federal public health emergency period of the COVID-19 pandemic. The results revealed a
significant strong positive relationship between intrinsic motivation and resilience and a
moderate positive relationship between risk-taking and resilience, flexibility and resilience,
tolerance of ambiguity and resilience, divergent thinking and resilience, originality and
resilience, fluency and resilience, resistance to premature closing and resilience, and convergent
thinking and resilience. A significant weak positive relationship was found between elaboration
and resilience. Results indicated that flexibility, intrinsic motivation, and risk-taking significantly
predicted resilience. No significant relationship was found between extrinsic motivation and
resilience. The absence of a significant relationship may have been due to temporal factors, and
measuring the predictive relationship between extrinsic motivation and resilience at a different
time may have revealed a significant relationship. Another reason for the absence of a significant
relationship may include differential factors. Extrinsic motivation is driven by external rewards,
and resilience involves intrinsic motivation, which comes from internal factors such as personal
values or a sense of purpose (Reisman et al., 2016). These internal factors may have a
moderating or mediating role in the connection between extrinsic motivation and resilience.

116
True nearly all
the time
In prior studies, several scholars supported the idea that the intersection of creativity and
resilience contributed to overall well-being, meaning-making, and adaptation to adversity
(Arnout & Almoied, 2020; Dunn, 2020; Kapoor & Kaufman, 2020). Unlike prior studies that
determined that resilience predicted creativity (Arnout & Almoied, 2020), the results of the
current study expand theory by identifying the predictive relationship of creativity and resilience.
Positive adaptation, as seen in the VUCA model of vision, understanding, clarity, and
agility, promoted stability, flexibility, and insight (Bywater & Lewis, 2019; Dima et al., 2021). In
prior studies, flexibility and tolerance for ambiguity were key factors that assisted in navigating
and coping with uncertainty and change, allowing creativity to emerge (Arnout & Almoied,
2020; Brendel et al., 2016; Skjei, 2014). Flexibility, the ability to quickly adapt to changing
situations and environments, was considered a competency of agility in VUCA environments
(Bywater & Lewis, 2019; Dima et al., 2021; Joiner & Josephs, 2006). Resilience and creativity
arise from creating solutions to adverse conditions to enable one to improvise, adapt, and survive
(Dunn, 2020; Richards, 2007; Weston & Imas, 2018). The results from the current study confirm
these findings and further identify flexibility and tolerance for ambiguity as creativity factors that
significantly correlate with resilience. Flexibility and tolerance for ambiguity enable individuals
to adapt more effectively to changes and uncertainties. In the face of unexpected events or
challenges, individuals with these qualities are better equipped to adjust their perspectives,
approaches, and strategies (Arnout & Almoied, 2020). Tolerance for ambiguity involves the
ability to tolerate, manage, and navigate situations that lack clarity or have ambiguous
information. This skill is essential in times of uncertainty, such as facing unforeseen

circumstances or dealing with complex problems (Weston & Imas, 2018). The results of the
current study support the need for flexibility in managing VUCA environments and expand the
concept of creative resilience to include predictive factors of intrinsic motivation and risk-taking.
The subfactors of creativity, tolerance of ambiguity, divergent thinking, originality,
fluency, resistance to premature closing, convergent thinking, and elaboration further delineate
important factors of creative resilience as demonstrated by their significant relationship to
resilience. The ten subfactors of the RDCA significantly correlated with resilience, creating a
new paradigm for identifying protective factors of creative resilience. These factors create a
comprehensive framework for understanding creative resilience. Tolerance of ambiguity provides
the foundation for navigating uncertainty, while divergent thinking, originality, fluency,
resistance to premature closing, convergent thinking, and elaboration contribute to the
development of innovative and adaptive responses to challenges. By integrating these elements,
individuals can cultivate creative resilience, enabling them to thrive in volatile, uncertain,
complex, and ambiguous environments.
Limitations
The study had several limitations, including construct, internal and external validity,
temporality, sampling, and data analysis. Regarding construct validity, participants may have
engaged in hypothesis guessing, making assumptions about what was being researched and based
their responses accordingly (Trochim, 2020). Participants’ anonymity was preserved, and
instructions delineated no wrong or correct answers. The research hypothesis was included in the
informed consent and may have affected responses (Black, 1999; Trochim, 2020). Internal
validity was low, since this survey-based descriptive correlational research study reflected

118
True nearly all
the time
relationships naturally existing within real-world settings (Trochim, 2020). Other known and
unknown variables may explain the significant relationships found (Field, 2018).
A census sampling and snowball approach was used to strengthen external validity yet
yielded a homogenous sample of primarily White female practitioners in private practice.
Findings from a homogeneous sample may have limited generalizability to larger and more
diverse populations (Black, 1999). Specific location data were not collected from participants,
which may have compromised external validity. The United States is diverse in geography,
culture, and socioeconomic factors; without location data, the survey may not capture regional
nuances and differences in opinions or behaviors. The temporality of COVID-19 also presented a
limitation in the timing of data collection. The research questions were critical and dependent on
the positionality of mental health providers as they relied on memory to reflect on their
experiences during the federal emergency period of COVID-19.
A limitation is the inability to conduct factor analysis due to an insufficient sample size.
Data analysis would have been strengthened with a larger sample size, enabling factor analysis
and/or stepwise regression. The data were not normally distributed, namely heteroscedastic,
which required alternative weighted regression analysis.
Recommendations
The current study confirms and extends existing methodological, theoretical, and
empirical implications. Methodological implications included the creation of a combined VUCA
variable consisting of individualized questions related to volatility, uncertainty, complexity, and
ambiguity. As VUCA environments continue to arise, researchers could use the questions

delineating experiences of volatility, uncertainty, complexity, and ambiguity in future studies to
investigate VUCA subcomponents. The application of VUCA as a theoretical model has not been
widely researched within the mental health field and among providers. The VUCA questions
created for the current study contribute to the field and provide a methodological basis for future
investigation that could enable organizations to identify, understand, navigate, and leverage the
complexities inherent in VUCA environments.
The current study extends existing theory with a novel approach to examining creativity,
task creativity, and the relationship between creativity and resilience in mental health providers
who experienced VUCA during the COVID-19 pandemic—further understanding how
environments are perceived as VUCA can aid future research and evidence-based, replicable
response efforts. The study findings confirm the existence of VUCA environments and
specifically identified COVID-19 as a VUCA environment, extending existing research in the
field theorizing that the pandemic yielded VUCA environments (Baskin & Bartlett, 2021; Fish &
Mittal, 2021; Sklar et al., 2021). The current study also indicated a significant positive
relationship between VUCA and creativity, contradicting the existing theory that VUCA
environments decrease creativity (Krauter, 2019). This concept extends the theories of creativity
emerging as a method for problem-solving during adverse times (Arnout & Almoied, 2020;
Dunn, 2020; Kapoor & Kaufman, 2020). The theoretical concept of creative resilience was
further developed in the study, as creativity predicted resilience with noteworthy factors of
flexibility, intrinsic motivation, risk-taking, tolerance of ambiguity, divergent thinking,
originality, fluency, resistance to premature closing, convergent thinking, and elaboration.
The empirical implications of the current study have practical significance for various
stakeholders, including practitioners, policymakers, and the broader community. The findings

120
True nearly all
the time
from the current study identified creativity as a predictor of resilience, which has important
implications for the field and can assist in fostering provider care and sustainability. Resilience is
crucial for effectively managing crises and unexpected challenges. Creative problem-solving
skills can be instrumental in navigating crises, allowing mental health providers to maintain
stability and continue providing support to those in need.
Creative tasks predicted resilience in the current study. Integrating creative approaches
into training curricula may enhance resilience-building skills and better prepare individuals for
the demands of their profession. Clinical training and education for therapists in the therapeutic
effects of creativity could enhance their own self-care practices and increase client referrals to
creative art therapists for treatment. Therapists could benefit from the ability to increase their
professional quality of life and agility in managing complex environments inherent in their work.
Furthermore, clinical treatment for emotional dysregulation, trauma, and anxiety could be
supported by assisting clients in managing uncertainty and tolerating ambiguity through creative
practices and coping skills such as flexibility, intrinsic motivation, risk-taking, and tolerance of
ambiguity—noteworthy creative factors of resilience.
Interventions that include task creativity can serve as accessible self-care strategies to
teach, inform, and train providers and organizations to build resilience. Workshops,
presentations, leader-driven and culture carrier incentives to bring innovative thinking and
creative resilience to the workforce could enhance productivity, innovation, and satisfaction.
Creative tasks can be fostered through a variety of approaches, including art-making workshops
that introduce creative concepts and the provision of spaces and time for artistic creation at work,

as well as guidelines for at-home practice. Art appreciation, including museum and gallery
viewings, concerts, and theater, could further enhance and stimulate one’s creativity. Creative
tasks are accessible and can be chosen based on the subjective choices of the individual, allowing
for cultural intersectionality. Potential barriers could include art being seen as elite by cultural
and historical perspectives, which could influence provider engagement (Yoeli et al., 2020).
Inversely, adults who have not practiced art-making since childhood could find it infantilizing
and may have resistance to engaging in art-making practices.
The finding that creativity predicts resilience can inform training and educational
programs for mental health providers. Creative mental health providers may be more likely to
develop and implement innovative treatment approaches. Innovation can lead to the discovery of
novel interventions that address the complex needs of clients, contributing to advancements in
the field. Creativity as a predictive factor of resilience needs to be evident in published
pandemic-related literature, which creates an opportunity for the current study to contribute to
the field of resilience in mental health care providers.
Creativity subfactors and positive professional quality of life were identified in the
current study as predictors of resilience. Secondary traumatic stress was negatively related to
resilience. Based on these findings, training and supervising providers and leaders within
systems of care to increase creative thinking, problem-solving, and task creativity can serve as
protective factors in mitigating negative professional quality of life and secondary traumatic
stress. Negative professional quality of life is an important concern in the mental health field.
The findings of the current study indicate that creativity is predictive of resilience, suggesting
that fostering a creative mindset may serve as a protective factor against burnout, helping
providers navigate the demands of their work without succumbing to exhaustion or

122
True nearly all
the time
disillusionment. Mental health providers often work in challenging and emotionally demanding
environments. Fostering creativity among providers can contribute to their overall well-being
and ability to cope with the stressors inherent in their roles.
Suggestions for Further Research
As the impact of the COVID-19 pandemic continues to be researched, recommendations
for future research include further exploration of VUCA environments, provider quality-of-life
issues, creativity, and resilience. Replicating this study within other VUCA environments, with a
large enough sample size to support factor analysis, could provide further insight into factors of
creativity that predict resilience. A larger sample size could also address threshold effects
encountered in this study by attaining the critical data points needed to examine relationships
between VUCA and resilience. The scales used to measure professional quality of life and
secondary traumatic stress might not have been aligned in terms of sensitivity, preventing the
detection of weak relationships. Replicating this study to measure professional quality of life and
secondary traumatic stress more sensitively with validated instruments, such as the ProQOL
(Stamm, 2010), could result in detecting weak relationships.
In the current study, secondary traumatic stress did not moderate the relationship between
creativity and resilience. This finding was interesting, as it suggests that secondary traumatic
stress did not contribute to the relationship between creativity and resilience, despite the presence
of adversity. Creativity continues to predict resilience within a VUCA environment. Future study
could focus on creativity as a protective factor against secondary traumatic stress using a variety

of methods, including randomized controlled studies to investigate the effectiveness of creative
thinking and practices and qualitative research to explore the essence of the lived experience.
A replication of the study with mental health providers during a psychological first aid
response, such as working with communities following a disaster, would enable real-time data
collection and reduce the issues of temporality encountered in the current study. Examining the
experience of VUCA, creativity, and resilience during the crisis with follow-up data collection
post-crisis could indicate change over time. In the current study, creativity predicted resilience in
the VUCA environment of COVID-19; extension of the research could include other
nonCOVID-19 VUCA environments to determine if creativity can predict resilience in other
contexts. The approach would be beneficial in adding to the understanding and management of
VUCA environments and the efficacy of creativity as a protective factor. Further research on
emerging socioeconomic change environments and how they are experienced as VUCA
environments could contribute to developing a model of approach and management.
Extending the current study to include a comparative between-group analysis would be
beneficial in determining if there is a difference in resilience in various populations. Mental
health practitioners were the population of focus in the current study, and creative art therapists
comprised more than 14% of the sample. Conducting comparisons by provider position, years in
the field, age, and work setting may reveal differences in provider creativity and resilience.
Additionally, the current study could be replicated to see whether the relationship between
creativity and resilience was significant in other populations, such as business, medical, and
educational providers. Between-group comparisons and replication studies would be beneficial in
determining if creative art therapists had higher levels of creativity than other mental health
providers. Conducting between-group comparisons and replication studies could reveal

124
True nearly all
the time
differences in the experiences of professional quality of life, creativity, and resilience within
alternative populations, such as those in medical, educational, and business contexts. The
findings from such studies could contribute to methods of training for mental health care
providers and support the further development of the field of creative art therapies.
In the current study, task creativity significantly predicted resilience. Further research is
recommended on how task creativity predicts resilience using comparative, experimental design.
This approach would allow for control groups and interventions using creative activities, such as
artmaking, music, and/or craft, to determine which activities contribute to resilience. Providers
would benefit from training on predictive factors that could increase resilience and decrease
susceptibility to secondary traumatic stress. Further research is suggested in qualitative inquiry,
which would allow for exploration of lived experiences, such as social isolation, lockdowns
during quarantine, and access to materials, and how these contribute to creative pursuits.
Creative subfactors significantly predicted resilience in the current study. Further detailed
research is recommended on the specific predictive factors of flexibility, intrinsic motivation, and
risk-taking as hallmarks of creativity and resilience. Identifying how these attributes could be
taught to providers, leaders, and systems to promote provider resilience and support
sustainability is critical. Further exploration of trait-based creativity in relation to creativity,
resilience and VUCA is recommended. Additional research can be conducted to explore the
influence of creative factors on resilience, aiming to uncover protective elements for mental
health care providers. This can help fortify efforts in preventing secondary traumatic stress and

mitigating negative impacts on professional quality of life, thereby supporting the resilience of
this crucial workforce.
Summary and Conclusion
The purpose of this quantitative predictive correlational study was to examine the
predictive relationship between creativity and resilience in mental health providers who
experienced VUCA while working in the United States during the federal public health
emergency period of the COVID-19 pandemic, which began on January 31, 2020, and ended on
May 11, 2023 (Silk et al., 2023). In order to adapt to and navigate volatile, uncertain, complex,
and ambiguous (VUCA) environments, such as the COVID-19 pandemic, it is necessary to
generate resiliency within self and the collective system. Identifying factors of creativity that
contribute to resiliency can mitigate secondary traumatic stress symptoms in mental health
providers.
The current study confirmed prior theoretical research and determined that mental health
workers experienced the COVID-19 pandemic as a VUCA environment. The findings indicated a
significant positive relationship between creativity and resilience, where multiple subfactors of
creativity contributed to resilience. Engagement in creative tasks during the pandemic
significantly predicted resilience. Participants reported that the pandemic affected their
professional quality of life, and negative experiences such as compassion fatigue, burnout, and
moral injury contributed to secondary traumatic stress symptoms. Positive professional quality of
life, such as compassion satisfaction, mattering, and a sense of purpose, was also evident and was
negatively correlated to secondary traumatic stress.
The findings indicated a significant positive relationship between creativity and
resilience, where multiple subfactors of creativity, including flexibility, intrinsic motivation,

126
True nearly all
the time
risktaking, tolerance of ambiguity, divergent thinking, originality, fluency, resistance to
premature closing, convergent thinking, and elaboration, contributed to resilience.
Recommendations for future research include further study on VUCA environments and
experimental research that incorporates creativity to promote provider well-being and increase
resilience. Implications of the study include identifying methods to study VUCA and promoting
creativity in providers to increase resilience and mitigate secondary traumatic stress.
USA

