


Well-being and Burnout in Psychologists 1
Well-being and Burnout in Psychologists
Abstract
Objective: Burnout among healthcare professionals is an increasing concern
due to adverse outcomes for clinicians, clients, and organisations (Bridgeman
et al., 2018; Azoulay et al., 2020). One identified systematic review
(McCormack et al., 2018) has explored burnout in psychologists and
psychological therapists; however, no identified reviews have focused solely on
psychologists. This review aimed to investigate the prevalence, causes and
factors associated with burnout in psychologists.
Method: Studies related to burnout in psychologists, published before
September 2021, were obtained from multidisciplinary databases. The search
yielded 582 papers, 26 papers were eligible for review. Researchers conducted
a thematic synthesis (Nicholson et al., 2016). Final themes were developed by
identifying commonalities across the sub-themes from separately grouped
qualitative and quantitative studies.
Findings: Psychologists experienced moderate to high levels of burnout related
to emotional exhaustion. Narrative synthesis highlighted three themes
concerning burnout-related factors: age and gender, occupational experiences
such as job demands, and personal resources such as humour and beliefs

Well-being and Burnout in Psychologists 2
about burnout. The development of support networks was found to be an
important protective factor for the included psychologists.
Conclusions: Emotional Exhaustion (EE) may play a key role in psychologists'
experiences of burnout, and further research relating to the experiences of EE
in younger and recently qualified psychologists may help to inform prevention
and intervention strategies.
Keywords: psychologists, burnout, emotional exhaustion, systematic review.
Introduction
Like many healthcare practitioners, psychologists may experience
burnout during their careers (Turnbull & Rhodes, 2021). The increasing concern
regarding burnout in healthcare populations is rooted in adverse personal and
occupational outcomes (Bridgeman et al., 2018). Burnout can lead to poor
mental health in healthcare workers (Morse et al., 2012); however, its impact is
not limited to the individual. Poor patient outcomes (Hall et al., 2016) and
interpersonal difficulties with colleagues (Guidroz et al., 2012; Vincent et al.,
2019) have also been associated with burnout. Burnout significantly contributes
to the absenteeism, retention, and recruitment costs healthcare providers face
(Kirby., 2023).
Psychologists comprise the most significant proportion of the NHS
psychological professions workforce at over 40% (HEE., 2021). The Mental
Health Implementation Plan proposed ambitious plans to recruit 2,520
additional psychologists into the workforce by 2024 (HEE., 2021) to meet the
demand for psychological interventions in the NHS (Iqbal et al., 2021). Despite
this, burnout in UK-based psychologists is under-researched. Understanding

Well-being and Burnout in Psychologists 3
psychologists' burnout experiences is imperative to supporting psychologists,
teams, clients and the ongoing expansion of the psychological workforce.
This review synthesised international literature relating to burnout in
psychologists. The conceptualisation and measurement of burnout are briefly
explored alongside research concerning burnout among psychologists.

Well-being and Burnout in Psychologists 4
Burnout
Burnout was introduced in 1975 as a work-related stress condition in
healthcare volunteers, resulting from long-term exposure to work-related stress
(Freudenberger, 1975). Maslach and colleagues later described burnout as a
state precipitated by a prolonged period of chronic emotional and interpersonal
workplace stressors (Maslach et al., 2001). Burnout is characterised by three
dimensions; exhaustion, cynicism, and inefficiency (Maslach et al., 2001).
Exhaustion represents the depletion of emotional and physical resources.
Cynicism, or depersonalisation, reflects the individual's negative or critical
responses towards their job, clients and colleagues, whilst reduced efficiency
refers to feelings of incompetence or lack of personal achievement.
Maslach's (1982) model of burnout led to the development of the
Maslach Burnout Inventory (MBI; Maslach et al., 1997), a 22-item self-report
tool designed to measure the presence of the three dimensions of burnout. The
MBI is well-validated and has been adapted to several other languages and
populations (Pisanti et al., 2013; Dolan et al., 2015). Despite being considered
the gold standard in burnout measurement (Williamson et al., 2018), the MBI is
not the only measure used in research. The MBI is based on Maslach’s three
dimensions; however, other proposed dimensions can be used to measure
prevalence. The Copenhagen Burnout Inventory (CBI) (Kristensen et al., 2005),
for example, identifies the presence of burnout by using three different
dimensions of burnout: personal, work-related, and client-related. Edú-Valsania
and colleagues (2022) provide a comprehensive review of burnout
measurement that is out of the scope of this review. It is, however, essential to
acknowledge that researchers' choice of burnout tools is crucial. It significantly

Well-being and Burnout in Psychologists 5
impacts how burnout is conceptualised, the aspects of experience being
measured, and the potential interpretation and impact on proposed
interventions.
Burnout in Psychologists
Psychologists are at a high risk of work-related emotional distress and
burnout (Kumary & Baker, 2008; Emery et al., 2009; Di Benedetto & Swadling,
2014). This is partly due to the intensity of the emotional experiences that
constitute their daily working life, including witnessing distress, trauma, and loss
(Rabu et al., 2016; Wise & Barnett., 2016). High caseloads, long waiting lists,
and high levels of autonomy have all been identified as additional work-related
stressors for psychologists (Johnson et al., 2012; McCormack et al., 2018).
Though these differ cross-culturally, long wait times (Kowalewski et al., 2011;
Olver et al., 2011; Ofonedu, et al.,2017; Punton et al., 2022), difficulties with
recruitment and retention (Fukui, & Salyers., 2019; Cosgrave., 2020), and
increasing demand are challenges faced by psychologists internationally. The
accumulation of these challenges can contribute to the experience of burnout.
Burnout is associated with significant adverse outcomes. Evidence
suggests that burnout can negatively impact quality of life and is positively
correlated with anxiety and depression (Morse et al., 2012), suicidal ideation
(Dyrbye et al., 2008), and emotion dysregulation (Gorgievski & Hobfoll, 2008;
Toh et al., 2012). Burnout poses a severe threat to healthcare providers as
burnout can 'transfer' between colleagues (Westman & Bakker., 2008 pp 1),
leading to poorer outcomes for patients (Hall et al., 2016) and increased levels

Well-being and Burnout in Psychologists 6
of clinical errors (Wilkinson et al., 2017). At an organisational level, burnout is
associated with increased absenteeism (Johnson et al., 2018), occupational
disengagement (Millar., 2018) and job withdrawal (Sheather & Slatter., 2021).
Lastly, the increased levels of staff sickness related to burnout (Summers et al.,
2021) and the subsequent impact on the retention and recruitment of staff
contribute to the growing financial crisis related to the retention and recruitment
of NHS staff, such as psychologists (Kirby., 2023).
Not only are psychologists expected to manage the pressures and
demands described, but unlike many other healthcare professions, they are
also expected to provide interventions to support the well-being of their teams
and reduce burnout (Heneghan et al., 2014; BPS., 2017). In addition,
psychologists hold leadership and management responsibilities alongside their
clinical workload (Channer et al., 2018). Though this varies, this is often not the
case for the healthcare workers with whom psychologists are grouped within
the research, e.g., mental health practitioners. There is also evidence that
psychologists may experience mental health stigma related to a perceived
expectation to know how to cope, which could negatively impact supportseeking
(Tay et al., 2018). The research does not provide insight into the specific
impacts of these factors concerning burnout; however, it is reasonable to
suggest that these additional demands mean that psychologists' experience of
burnout may differ somewhat from their healthcare colleagues. As such, the
experiences of psychologists must be considered independently of their
healthcare colleagues to allow researchers to identify specific experiences and
needs of the population.

Well-being and Burnout in Psychologists 7
Review Rationale
Burnout in psychologists is a complex issue that can be impactful at
individual, service, and organisational levels. To the researcher's knowledge,
only one systematic review, that of McCormack and colleagues (2018), has
explored burnout in psychologists capturing data published before 31st
December 2016. The proposed review may capture research published
between 2016 and 2022, thus providing a beneficial updated picture in relation
to the prevalence factors and causes of burnout in psychologists. An updated
review would also capture the influx in research around burnout resulting from
the impact of the Covid-19 pandemic on healthcare workers (Gonda & Tarazi.,
2022). In addition, although McCormack et al. (2018) did capture burnout in
psychologists, they also included allied mental health practitioners in their
population samples (McCormack et al., 2018). Thus the population sample is
relatively broad. By narrowing the inclusion criteria, this review can draw
conclusions specifically relating to the experience of psychologists who may
have different burnout experiences and needs compared to their
multidisciplinary colleagues. As such, recommendations can be tailored
specifically to the needs of psychologists.
To the researcher's knowledge, there do not appear to have been any
attempts to explore the research relating specifically to professional
psychologists, including data published between 2016 and 2022. For
transparency, the researcher broadened the search for existing literature
reviews to cover any published reviews exploring burnout-related concepts,
such as compassion fatigue and emotional exhaustion. Though the search did

Well-being and Burnout in Psychologists 8
yield a systematic review exploring compassion fatigue in healthcare workers
(Cavanagh et al., 2020), the population here included a broad range of
healthcare workers, with only two of the seventy-one included papers including
psychologists in their sample. A search of the Cochrane Databases yielded no
registered reviews intending to collate the proposed review question.
Review Aims and Objectives
The current paper aims to systematically review international research
regarding the causes and prevalence of burnout among psychologists.
Examining the existing research may support researchers and clinicians to
better understand the development process and potentially nuanced
experiences of psychologists. Thus, potentially leading to more appropriately
informed prevention and intervention strategies. This systematic review aims to
answer the following questions:
1. What is the prevalence of burnout among psychologists?
2. What are the causes and factors related to burnout in psychologists?
Method
Design
This paper describes a mixed-methods systematic literature review. The
Joanna Briggs Institute Clinical Appraisal Tools (JBI) (Joanna Briggs Institute,
2017) were selected to appraise the included studies' methodological rigour and
highlight potential areas of caution when interpreting the findings. A narrative,
thematic synthesis (TS) was used to analyse the identified studies to enable the
Well-being and Burnout in Psychologists 9
researchers to move beyond the original study findings and generate related
themes across the data (Thomas & Harden, 2008).
The Preferred Reporting Items for Systematic Reviews and
MetaAnalyses (PRISMA) (Page et al., 2021) guidance was used to ensure the
review was of sound quality and could be easily replicated (Appendix A).
Screening and Sampling
The SPIDER framework (Cooke et al., 2012) was adapted to
support the development of inclusion criteria and search terms.
Inclusion / Exclusion Criteria
An independent qualitative researcher and health psychologist consulted
with the researchers during the development of the inclusion criteria presented
in Table 1. Both quantitative and qualitative empirical papers were included.
Grey literature and papers not published in English were excluded. Though
peer review has not always ensured validity (Smith., 2006), grey literature was
excluded to support the review's rigour. Papers with samples of school
psychologists (SPs) were excluded to preserve the homogeneity of the sample,
as the SPs' training pathway and responsibilities differ significantly from other
registered psychologists (NASP, 2022). Papers focusing on interventions were
excluded as they fell outside the review scope.
Table 1
Inclusion and Exclusion Criteria
SPIDER Inclusion Exclusion

Well-being and Burnout in Psychologists 10
Sample Participants were trainee or qualified School Psychologists
psychologists
from one of six Pre-qualification
disciplines: clinical, health, psychologists
counselling, forensic, education or sport.
Phenomena of
Interest
One or more dimensions of burnout as
defined by the burnout tool utilised in the
study.
Design
Qualitative, Quantitative and Mixed
Methods research reporting on primary
data
Evaluation
Prevalence of burnout in the sample
Causal Factors relating to the
development or experience of burnout
Research
Type
Qualitative, Quantitative and Mixed Grey literature
Methods
Studies published in the English Existing literature, or
language. systematic reviews
Studies published in a peer-reviewed
journal. Publications not reporting
primary data
Search Terms
Search terms (STs), provided in Table 2, were developed in three stages:
1. A scoping search was carried out to generate key STs and test the
sensitivity and specificity of the search terms developed using SPIDER.
2. These were cross-referenced with the STs used in systematic reviews of
burnout in other healthcare professionals (McCormack et al., 2018;
Well-being and Burnout in Psychologists 11
O'Connor et al., 2018).
3. Consultation with the University of Exeter Psychology Liaison Librarian to
identify any database-specific medical subject headings (MeSH) terms to
improve the search strategy.
Terms relating to measurable outcomes were kept broad to reflect the
breadth of burnout dimensions. Greater sensitivity and specificity were applied
to the population terms. Search terms were applied to MEDLINE, PsychInfo,
and Webb of Science; MeSH terms and age filters were used in Medline and
PsychInfo only (Appendix B).
Table 2
Search Terms
2 Psychologist*
3 Stress*
4 Emotional exhaustion
5 Pressure
6 Coping
7 Manage
8 Well-being
9 Mental health
10 Work-related stress
11 Compassion fatigue
12 1 AND 2
13 3 OR 4 OR 5 OR 6 OR 7 OR 8 OR 9 OR 10 OR 11
14 12 AND 13
1
Burnout

Well-being and Burnout in Psychologists 12
Screening Procedure
Duplicate papers were identified using Rayyan Intelligent Systematic
Review software, checked manually, and then deleted. Next, titles and abstracts
were screened against the inclusion criteria, and those which did not satisfy the
requirements were rejected. As recommended by (Boland et al., 2017), the full
text of the remaining papers was then read, and papers which satisfied the
inclusion criteria were included for review. Lastly, following the National Institute
for Health and Care Excellence (NICE) (2012) guidelines for the compilation of
systematic reviews, the reference lists of all eligible papers were screened for
relevant papers not generated by the search strategy.
Data Extraction
A data extraction table was developed using the SPIDER framework,
discussions with the research team, and consideration of information pertinent
to the research questions. The table included sample characteristics, country,
study design, use of burnout measures, key findings and limitations (Appendix
C).
Quality Appraisal
Quality appraisals (QA) in mixed methods reviews can present
challenges due to the heterogeneity of the study designs (Hong et al., 2018).
The Mixed Methods Assessment Tool (MMAT) (Pluye et al., 2009a, Pace et al.,
2012, Hong et al., 2018) was developed specifically for use in mixed methods
reviews and was initially selected for this review. After completing QA on three

Well-being and Burnout in Psychologists 13
of the included papers, it became apparent that the MMAT did not capture some
of the nuances of qualitative design, such as the researcher's relationship to the
data. Additionally, the checklist format of the MMAT did not allow for descriptive
notes by the researchers, which was essential to ensure consistency of
judgement-making when reviewing a large number of studies. Alternative
options were explored, whereby papers could be assessed by tools specific to
the research design whilst maintaining some continuity of assessment quality
across the tools.
Based on this rationale, papers were assessed using analytical
crosssectional or qualitative JBI Clinical Appraisal Tools (Appendices D and E).
The JBI tools use a mix of multiple-choice and open questions to assess the
quality and allow for descriptive comments from the assessor (Joanna Briggs
Institute, 2017). Mixed-methods studies were appraised twice, once using the
appropriate quantitative checklist and then again using the qualitative checklist.
One point was awarded for each criterion fully met. Mixed methods papers were
awarded two scores. An independent researcher quality assessed six papers.
Inter-rater reliability was calculated using Cohen's kappa (k = 0.83).
Data Analysis
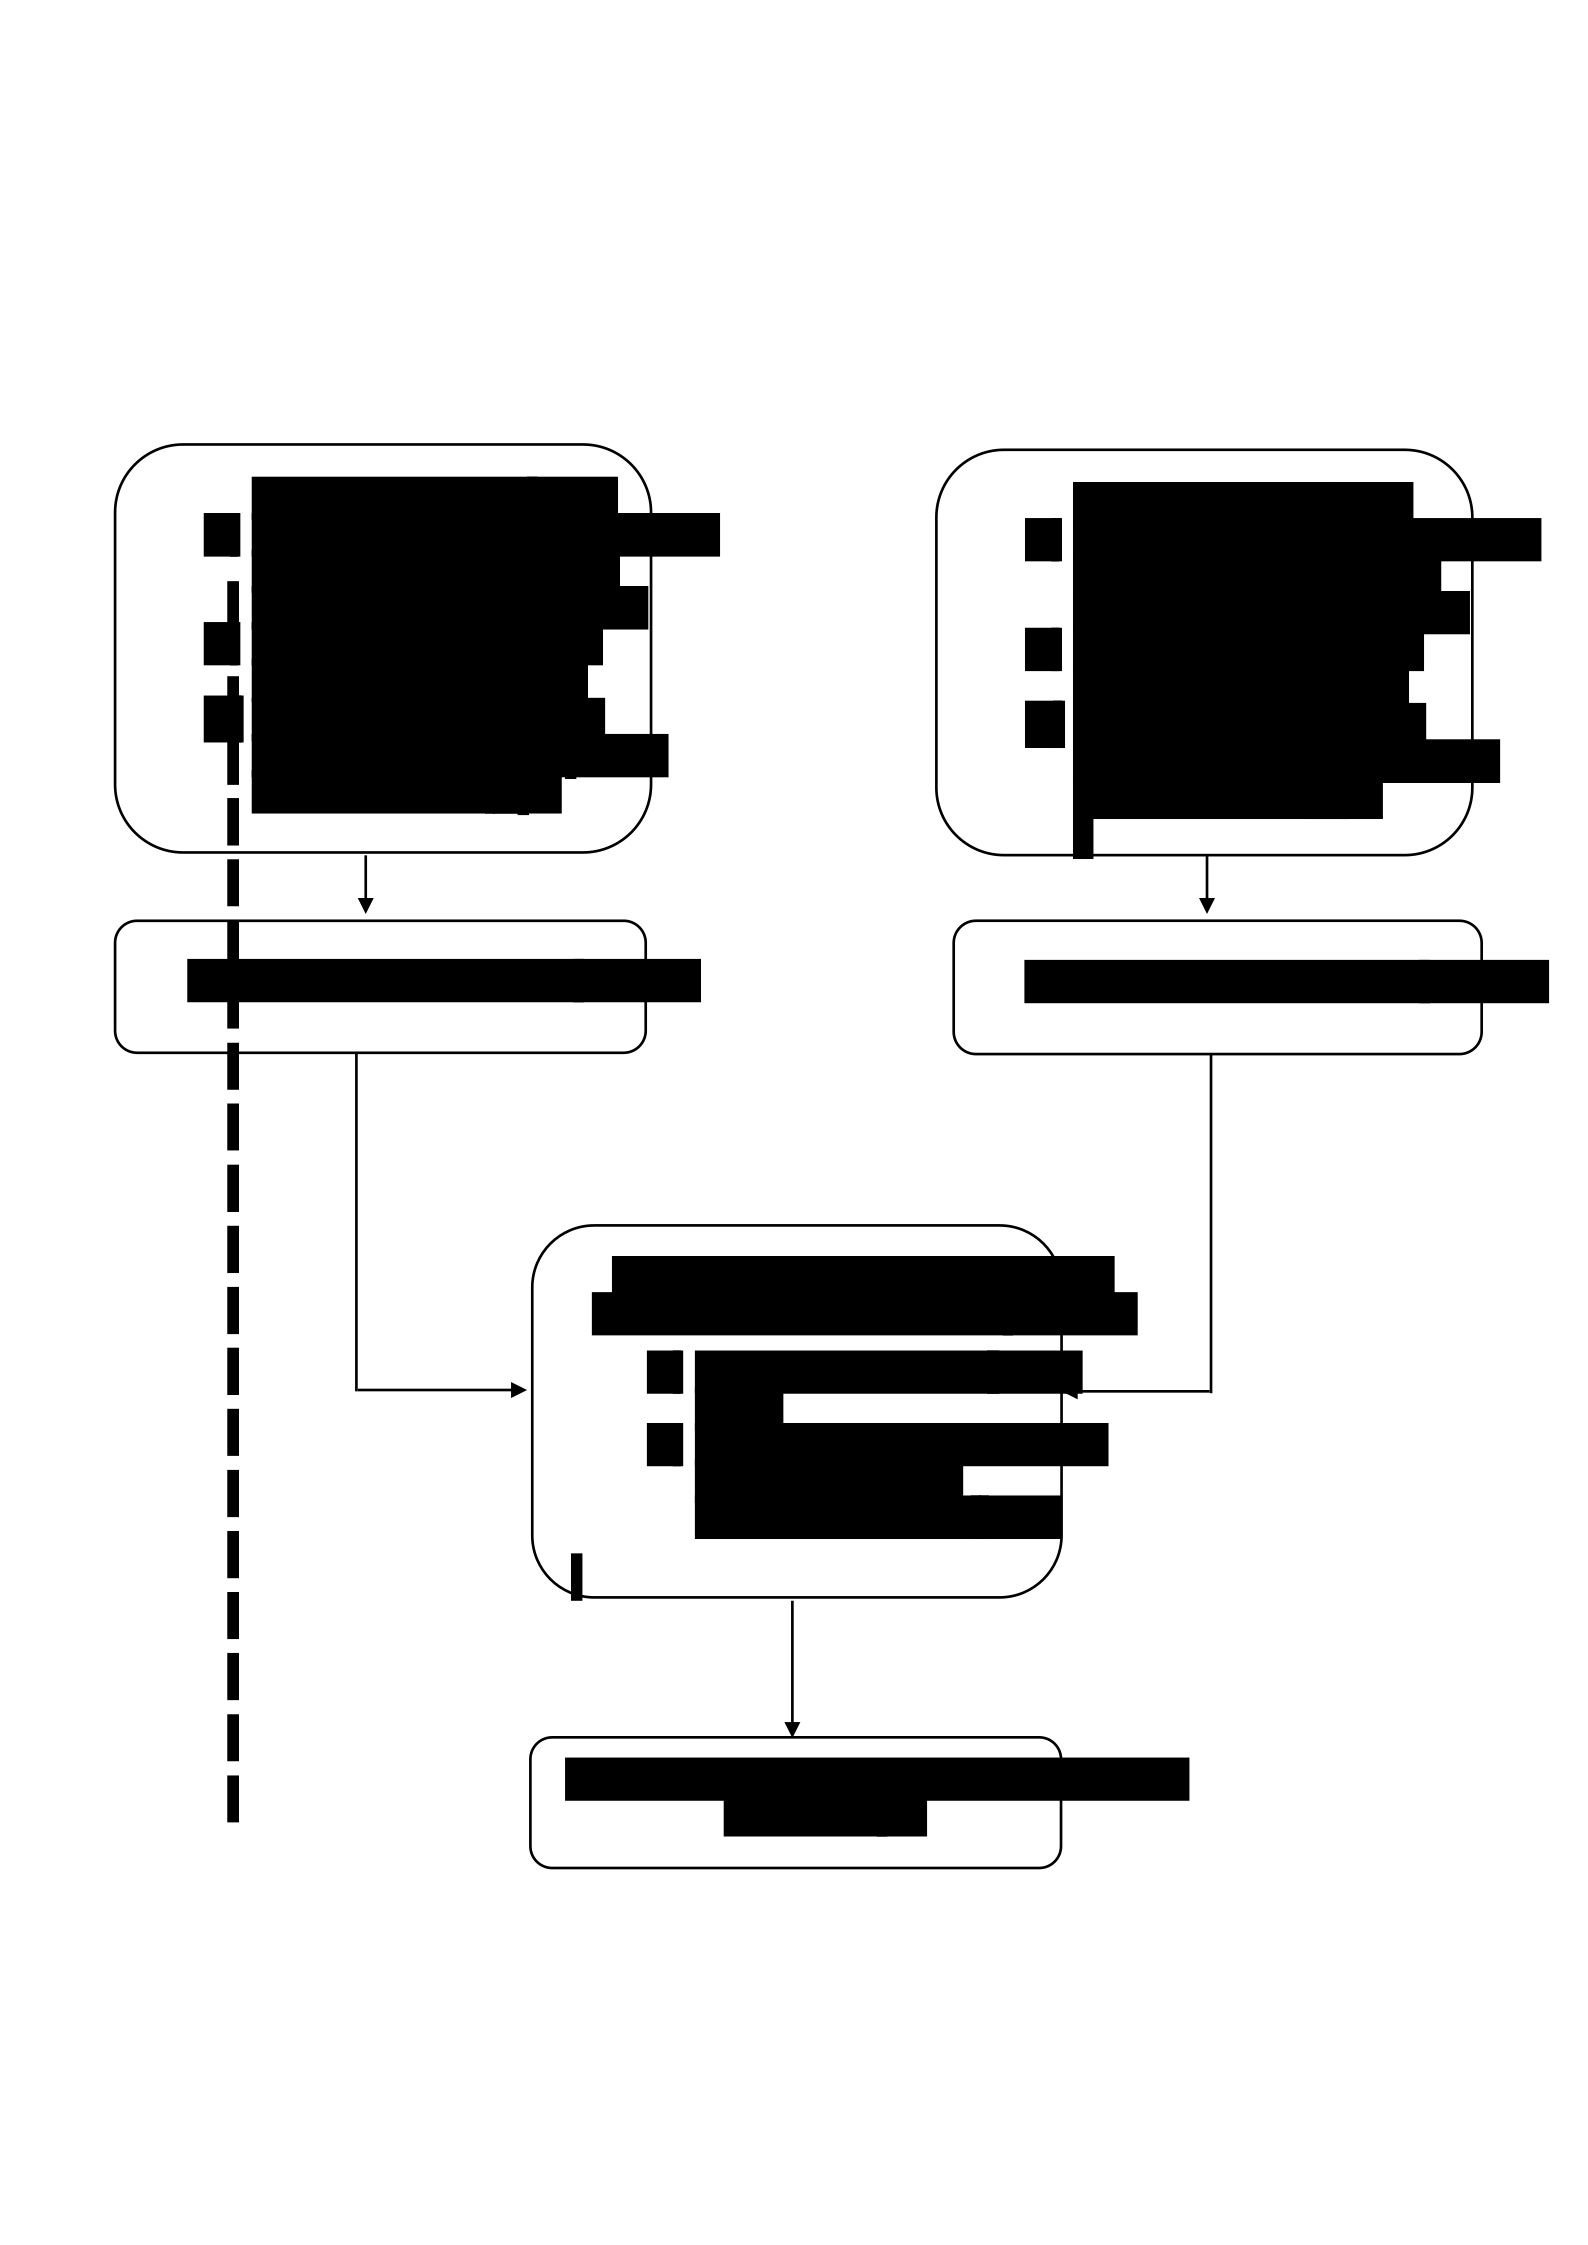
Thomas and Harden's (2008) thematic synthesis guidance was applied
to analyse the data and to develop descriptive and analytic themes (Figure 1).
TS was selected as it offers consistency across the analysis of qualitative and
quantitative data, is well suited to reviewing medium size data sets, and has
been successfully applied to mixed methods health-related literature reviews

Well-being and Burnout in Psychologists 14
(Dixon-Woods et al., 2005; Nicholson et al., 2016; Etkind et al., 2018; Ryan et
al., 2018). TS also encourages transparency, which is essential for the clarity
and quality of findings generated by synthesising data (Tong et al., 2012).
In line with Thomas and Harden's (2008) model, all data labelled results
or findings were extracted from the papers for analysis. The qualitative and
quantitative data from the mixed methods paper (#15) were separated and
analysed with the respective data. The analysis took place in three stages
(each stage applied to the quantitative data first and then to the qualitative
data). First, data was line-by-line coded, generating descriptive codes. Next,
codes were grouped into descriptive themes based on commonalities or
patterns in the data. Finally, to 'go beyond' the primary data (Thomas &
Harden., 2008), analytic themes were developed by critically reviewing the
descriptive themes in light of the research question. Once this process was
completed for both quantitative and qualitative papers, the analytic themes were
compared. Similarities and differences were identified, leading to an overall
account of the synthesis findings.
Well-being and Burnout in Psychologists 15
Figure 1
Summary of the data analysis process.
Quantitative Papers
1)
Line by line coding. Codes
closely related to the
content of the data set.
2)
Codes grouped into
descriptive themes.
3)
Analytic themes are
developed based on the
research question
.
Qualitative Papers
1)
Line by line coding. Codes
closely related to the
content of the data set.
2)
Codes grouped into
descriptive themes.
3)
Analytic themes are
developed based on the
research question
.
Overall Themes and Findings are
Generated
Analytic Themes Generated
Analytic Themes Generated
Integrating Qualitative and
Quantitative Analytic Themes
1)
Analytic themes are re
-
read.
2)
Themes are compared,
similarities and
differences are noted
.

Well-being and Burnout in Psychologists 16
Findings
In total, 721 papers were identified in MEDLINE, PsychInfo and Webb of
Science searches.
Data Screening
One hundred and thirty-nine duplicate papers were identified using
Rayyan Intelligent Systematic Review software, checked manually, and then
deleted. This left 582 titles and abstracts to be screened against the inclusion
and exclusion criteria. Four hundred and eighty-nine papers were excluded at
this stage. The remaining 46 papers were read in full, and twenty-five papers
met the full criteria for inclusion. A review of the reference lists of the included
papers identified six additional papers which were screened. One additional
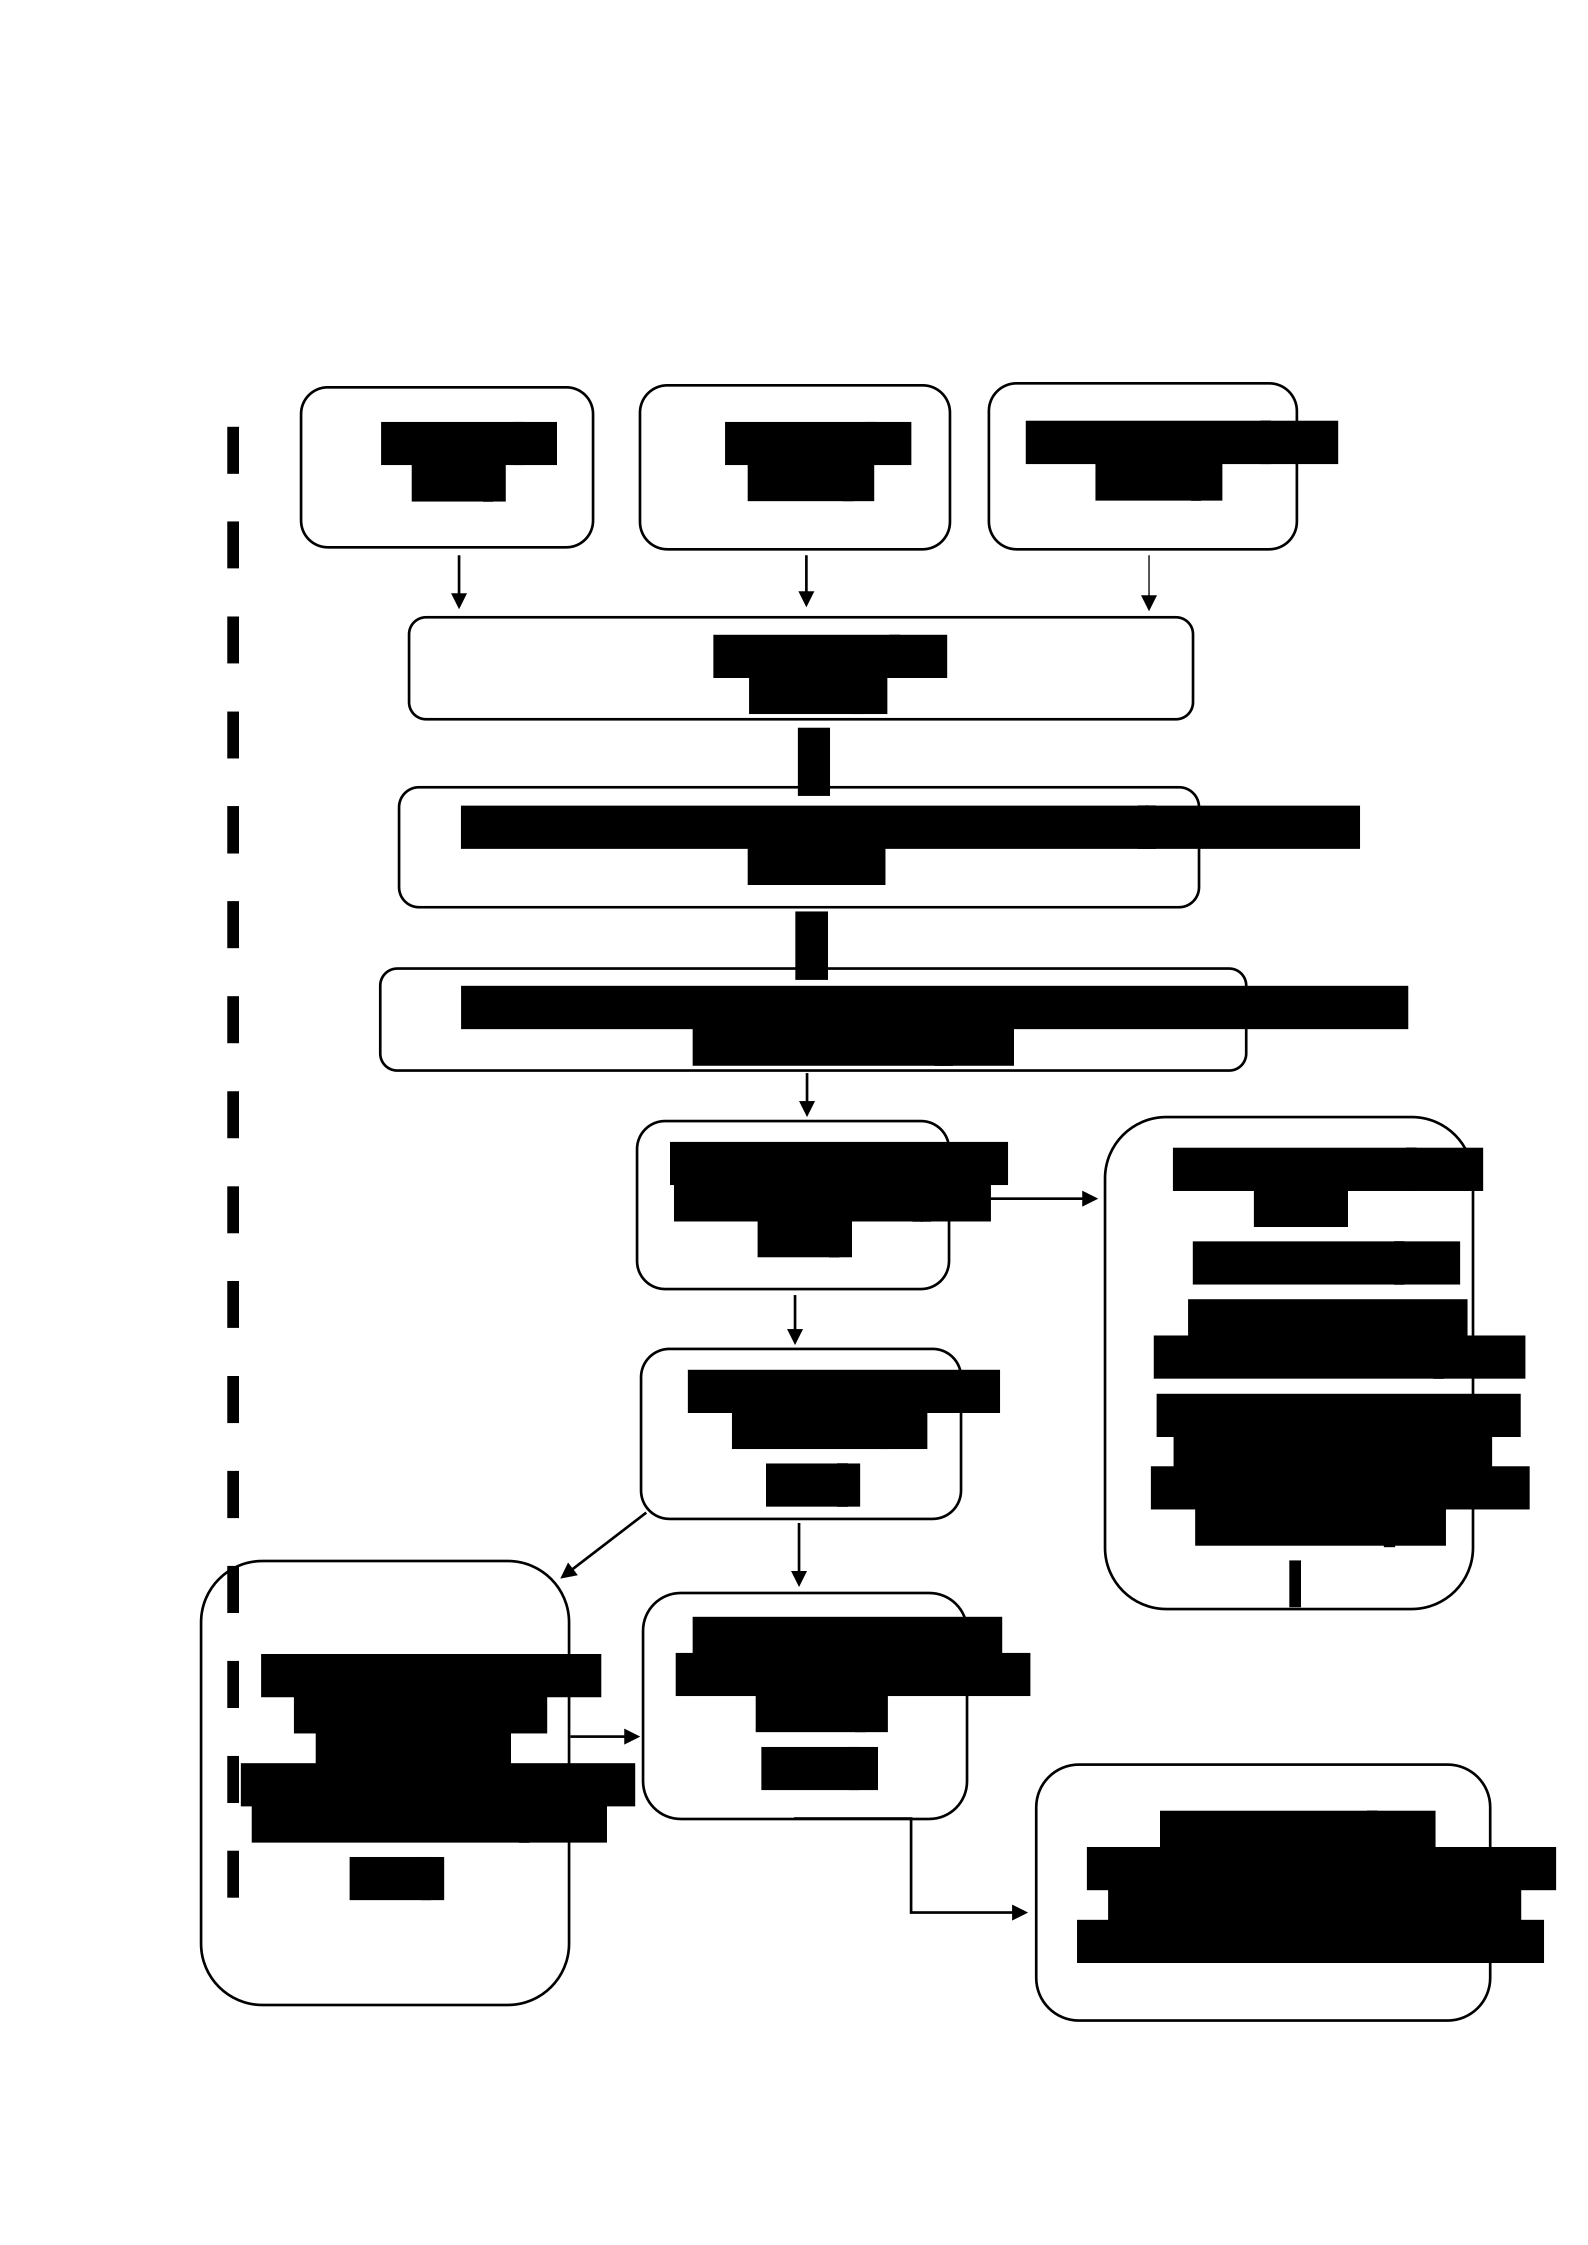
paper met the requirements, bringing the total number of eligible studies to 26
(full process provided in figure 2). A senior research associate at an
independent university screened six papers against the inclusion and exclusion
criteria. Inter-rater reliability was calculated using Cohen's kappa (k = 1).
Included papers are presented in Table 3, and a summary of key information in
Table 4.
Well-being and Burnout in Psychologists 17
Figure 2
Summary of the data sampling and screening procedure
PsychInfo
N= 437
Webb of Science
N= 218
Duplicates Identified and removed using Rayyan
N = 139
Title and abstracts screened against inclusion and
exclusion criteria
MEDLINE
N=66
Papers remaining
for full screening
N=46
Papers excluded
N=21
Duplicate N= 1
Participants not
psychologists N = 11
Wrong phenomenon
being studied (i.e.
stress not specifically
burnout) N = 9
Total Papers
N = 721
Papers included
for review
N=25
Additional papers
generated by
searching
references of papers
included for review
N = 1
Total Number of
papers included in
review.
N = 26
Methodologies
Quantitative Papers N = 20
Qualitative Papers N= 5
Mixed
-
Methods Papers N= 1

Well-being and Burnout in Psychologists 18
Table 3
Authors, publication year, titles of included papers and geographical population
in Alphabetical Order, by Author
Author and Year Title Title Geographical
of Publication Population
Ackerley et al., #1 Burnout among licensed USA and Canada
1988 psychologists
Allwood et al., #2 The relationship between Sweden
2022 personality, work, and personal
factors to burnout among clinical
psychologists: exploring gender
differences in Sweden
Berjot et al., #3 Burnout risk profiles among France
2017 French psychologists
Clarke et al., #4 The perceived effects of Australia
2021 emotional labour in psychologists
providing individual
psychotherapy
Di Benedetto #5 Burnout in Australian Australia and Swadling
psychologists: Correlations with
2014 work-setting, mindfulness and
self-care behaviours
D'souza et al., #6 The relationship between Australia
2011 perfectionism, stress and burnout
in clinical psychologists

Well-being and Burnout in Psychologists 19
Emery et al.,
2009
#7
Associations among therapist
beliefs, personal resources and
burnout in clinical psychologists
Australia
Hammond et al.,
2018
#8
A thematic inquiry into the burnout
experience of Australian solo-
practising clinical psychologists
Australia
Keading et al.,
2017
#9
Professional burnout, early
maladaptive schemas, and physical
health in clinical and counselling
psychology trainees
Australia, USA,
Canada, UK
Kahill., 1986
#10
Relationship of burnout among
professional psychologists to
professional expectations and
social support.
Canada
Malinowksi.,
2013
#11
Characteristics of job burnout and
humour among psychotherapists.
USA
McCade et al.,
2021
#12
Burnout and depression in
Australian psychologists: The
moderating role of selfcompassion
Australia
McCormack et
al., 2015
#13
Practicing what we preach:
investigating the role of social
support in sport psychologists' well-
being
USA, UK, Ireland,
Australia, New Zeland

Well-being and Burnout in Psychologists 20
Rodrigeuz and
Carlotto., 2017
#14
Predictors of burnout syndrome
in psychologists
Brazil
Roncalli and
Byrne., 2016
#15
Relationships at work, burnout
and job satisfaction: A study
on Irish psychologists.
Ireland
Rupert and
Kent., 2007
#16
Gender and work setting
differences in career-sustaining
behaviours and burnout among
professional psychologists
USA
Rupert and
Morgan., 2005
#17
Work setting and burnout among
professional psychologists
USA
Rupert et al.,
2009
#18
Work-family conflict and burnout
among practising psychologists
USA
Sadusky and
Spinks., 2022
#19
Psychologists' engagement in
reflective practice and
experiences of burnout: a
correlational analysis
Australia, UK and New
Zeland
Simpson et al.,
2019
#20
Burnout amongst clinical and
counselling psychologists: The
role of early maladaptive schemas
and coping modes as
vulnerability factors
Open Globally:
Countries listed
Australia, New
Zealand, UK,
Neatherlands, USA,
Canada and 'Others'
Sim et al., 2016
#21
Thriving, burnout, and coping
strategies of early and later career
counselling centre
USA
psychologists in the United
States

Well-being and Burnout in Psychologists 21
Skorupa and
Agresti., 1993
#22
Ethical beliefs about burnout and
continued professional practice
USA
Smout et al.,
2022
#23
The influence of maladaptive
coping modes, resilience, and job
demands on emotional exhaustion
in psychologists
Australia and UK
Turnball &
Rhodes., 2021
#24
Burnout and growth: Narratives of
Australian Psychologists
Australia
Vrendenburg et
al., 1999
#25
Burnout in counselling
psychologists: Type of practice
setting and pertinent
demographics.
USA
Williams et al.,
2020
#26
Psychologists' practices, stressors,
and wellness in academic health
centres.
USA

Well-being and Burnout in Psychologists 22
Table 4
Summary of Key Aims, demographics, and methodologies of included papers, in Alphabetical Order, by Author
Paper Aims Design and Participant Findings JBI Risk of Bias and Limitations
ID Method Demographics Score
#1
Examine the level of
burnout and correlates of
burnout.
ANOVA and
Multiple
Regression.
562 Doctoral
Level Licensed
Psychologists
73% Male
27% Female.
Reported that burnedout
clinicians were likely to
be young, low earners,
not engaged in
psychotherapy,
experienced feelings of
lack of control and were
over-involved with client
work.
6/8
Researchers do not state if this
gender split is representative of
the field. Psychologists
experiencing burnout may not
have responded to the request.
Cross-sectional data cannot
provide insight into causation.
#2
Investigate the effects of
gender, personality, job
demands, affective work
rumination and personal-
Hierarchical
multiple
regression
analyses
828 Clinical
Health
Psychologists
78% Female 22%
Male.
Many factors impact
burnout, including
gender, workrumination,
conflict, and exhaustion.
6/8
Inclusion/Exclusion criteria are
not clearly stated, and the period
for data collection is unknown.
Cross-sectional data cannot
provide insight into causation.

Well-being and Burnout in Psychologists 23
to-work conflict on
burnout.
#3 Identify profiles at risk of Hierarchical
burnout. cluster
analysis.
Twoway
ANOVA. 664
Qualified
Age, work
environment
, 7/8
Psychologists and work demands were
9.9% Male all associated with
90.1% Female. burnout in psychologists.
The population of people identifying with neither
gender was not large enough for analysis.
The sample may have overrepresented female
psychologists. Provide findings related to
seniority, but it's unclear what authors classify
seniority.
#4
To explore emotional
labour and burnout in
psychologists who
provide individual therapy.
Thematic
Analysis.
24
Psychologists
grouped into
Early career
psychologists
(N= 9), Mid-
Career
Psychologists
(N=7) and
Experienced
Psychologists
(N=8)
The increased emotional
intensity of clinical work
is linked to higher levels
of emotional exhaustion
and the need to distance
oneself from workrelated
emotions.
10/10
Did not capture the views of those
who may have left direct clinical
roles due to burnout. The sample
was restricted to western
Australia.

Well-being and Burnout in Psychologists 24
#5
To investigate the
relationships between
burnout, work-setting,
years of experience in that
setting, mindfulness, and
career-sustaining
behaviours (CSBs).
One-way
betweensubjects
ANOVA.
167 Registered
Psychologists
86.8% Female
13.2% Male.
Psychologists with less
time and experience in
their posts have higher
rates of burnout. Increased
mindfulness skills are
linked to lower levels of
burnout.
6/8
Recruitment through registration
bodies may not capture.
Psychologists who have burnt out
and may have left the profession
and no longer hold a professional
registration.
#6
To examine the relationship
between perfectionism,
stress and burnout.
Regression
Analysis.
87 Clinical
Psychologists
86% Female
14% Male
Perfectionism was directly
and indirectly related to
the development of
burnout.
7/8
Relatively small sample, not
adequate to conduct regression
analyses.
#7
To Examine the
contribution of
demographics, workplace
variables, and individual
factors to burnout.
Factor Analysis
and Multiple
Regression.
190 Clinical
Psychologists
71.6% Female
27.9% Male 5%
unaccounted
for.
Being female, working
for the government,
having fewer personal
resources, and having
beliefs about clients were
linked to higher levels of
emotional exhaustion.
7/8
Only 11-34% of the variance of
each burnout scale is accounted
for. Psychologists' level of
cognitive training was not
considered. Can't inform the
direction of the relationship, i.e.,
whether therapist beliefs and lack
of coping resources cause work
stress or vice versa.

Well-being and Burnout in Psychologists 25
#8
To examine the different
experiences of burnout
across Australian
psychologists.
Thematic
Analysis
6 Clinical
Psychologists
Psychologists reported
excessive workload and
hours of work, life
stresses, mismanagement,
and transference between
clients' and their
psychologists as factors
related to burnout.
9/10
Limited sample. Only recruited
participants currently practising,
missed the opportunity to capture
those who may have ceased
practice due to burnout.
No statement locating the
researchers culturally or
theoretically in relation to their
research.
#9
To explore the
Discriminant
1172 Clinical
High burnout was
6/8
Psychologists in this study were
relationship between Early
Maladaptive Schema
(EMS) and burnout.
function analysis
and
Counselling
Trainee
Psychologists
82.3% Female
17.7% Male
associated with a higher
level of physical health
problems and greater
endorsement of all Early
Maladaptive Coping
Styles, but only the
unrelenting standards
were found to be a
significant predictor of
burnout.
not screened for pre-existing
health conditions. The study was
subject to response bias, whereby
participants may have
underreported some EMSs and
endorsed EMSs they perceived as
culturally acceptable— concerns
about being labelled incompetent
etc.
#10
To explore burnout in
relation to social support
Pearson's
correlations
225 Trainee,
newly qualified
Burnout is significantly
related to social support
6/8
Limited sample from a small
geographical area. Inclusion

Well-being and Burnout in Psychologists 26
in private life and
expectations or attitudes
about the profession. To
compare burnout
experiences across varying
professional experience.
and univariate
ANOVA
and experienced
psychologists.
'Roughly equal'
proportions of
Male and
female.
from family and friends
and expectations or
attitudes about the
profession.
/Exclusion criteria are not stated.
Researchers have identified
confounding factors but do not
appear to have controlled for
these during the analysis.
#11
To explore the relationships
between types of humour
and characteristics of job
burnout.
Stepwise
Regression and
Bivariate
Correlation
Analysis
133
Psychologists
68.4% Female
31.6% Male
Self-defeating humour
contributed to higher
levels of emotional
exhaustion and
depersonalisation.
Selfenhancing humour
contributed to higher
levels of personal
accomplishment.
7/8
Using purposive sampling, those
who responded were likely to
have an interest or connection to
the research topic. Relationships
are moderate. Variables needed
to be transformed to perform the
statistical analysis, which may
have affected the outcome.
Causality cannot be determined.
#12
To examine the
relationships between self-
compassion, depression
and burnout.
Hierarchical
linear
regression.
259
Psychologists
40% Female
60% Male
Self-compassion
mediated levels of
burnout and depression in
psychologists. Higher
self-compassion was
linked to lower levels of
6/8
The cross-sectional study design
cannot comment on causality.
There may be other
explanations accounting for the
relationship
burnout and fewer depressive
symptoms.
between burnout, depression, and
self-compassion, not considered

Well-being and Burnout in Psychologists 27
in the research.
#13
To explore the experience
of burnout in sports
psychologists
Thematic
Analysis
30 Sports
Psychologists
Burnout is frequently
experienced despite
psychologists
experiencing high levels
of work engagement—
lower levels of social
support are associated
with higher levels of
burnout.
8/10
No statement positioning the
researchers or exploration of their
impact on the data collection and
analysis.
#14 To identify individual Multiple Linear
variables and job Regression
characteristics that can predict
burnout in Analysis psychologists.
(Stepwise)
518
Psychologists 1 year + postqualification
77% Female
23% Male
The strongest
factors linked
to burnout
dimensions
were
overwork and
emotionfocused coping
strategies. Burnout
occurs due to the
overlap of personal and
work-related variables.
6/8 A cross-
sectional design, which does not allow for
causal conclusions. Again, this highlights
the "healthy worker effect," which may
underestimate the magnitude of the
identified risks.

Well-being and Burnout in Psychologists 28
#15
Examine the levels of job
satisfaction and burnout
among psychologists
working in Irish community
mental health teams
(CMHTs).
Hierarchical
Regression
Analysis and
Thematic
Analysis
77
Psychologists
76.6% Female
23.4% Male
Relational aspects of
psychologists' jobs and
job satisfaction are
significant factors in the
development of burnout.
6/8
7/10
The low response rate and
consequent small sample size
limit the possibility of generalising
the results in terms of the
representativeness of the wider
population of CMHT
psychologists. The small sample
size also limited the choice of
data analyses that could be used,
prohibiting the reliable testing of
more comprehensive models.
Cross-sectional, no causal
relationships
#16
To examine gender
differences in burnout, work
activities and demands,
and work resources in
independent practice and
agency settings.
Analysis of
Covariance
(ANCOVA) and
Pearson
Correlations.
595
Psychologists
58.3% Female
41.7% Male
Female agency
psychologists experience
higher levels of
emotional exhaustion.
Working in agency
settings is associated
with higher levels of
burnout.
6/8
Did not include psychologists
whose primary work setting was
not clinical. It may have excluded
psychologists who had left clinical
fields due to burnout. Restricted
to clinical and counselling
psychologists may not represent a
wider discipline. Confounding
variables are not fully identified and
explained.

Well-being and Burnout in Psychologists 29
#17
To examine the
relationship between work
setting and burnout
Analysis of
covariance
(ANCOVA) and
Pearson
correlations.
571
Psychologists
54.3% Female
45.7% Male
Higher levels of
emotional exhaustion
were associated with
less control over work
activities, working more
hours, spending more
time on administrative
tasks and paperwork,
and engaging with
challenging clients
7/8
It doesn't define what is meant by
the different work groups. They
also don't explain how they
managed individuals who might
hold dual roles. One criterion was
identified as a clinical setting as
their primary place of
employment; they may not
capture psychologists who have
left clinical settings due to
burnout.
#18
To explore gender and
work-setting interactions
on emotional exhaustion
and work-setting
differences in resources
and demands that relate to
burnout
Analysis of
Covariance
(ANCOVA)
421
Psychologists
57.9% Female
42.4% Male
Family support was
important for workrelated
well-being; however,
conflict between work
and family domains was
associated with burnout.
7/8
The sample was majority white,
based on Eurocentric family
ideas.

Well-being and Burnout in Psychologists 30
#19
To investigate the
relationships between
psychologists' burnout
levels and reflective
practices.
Pearson's
Correlation
120 Qualified
Psychologists
83.3% Female
16.7% Male
Burnout was associated
with the level of job
satisfaction and stress
interacting with clients.
The importance of
adequate supervision
was highlighted as a key
finding.
6/8
The majority of respondents
were from Australia, making it
difficult to generalise to other
countries. Non-experimental
design of this study prevented
the researchers from
establishing causality or creating
a predictive model between RP
and burnout variables.
#20
To examine the work
setting, main sources
of stress, and
prevalence of burnout.
To identify the
predominant Early
Maladaptive Schema's
(EMS) and Maladaptive
Coping Modes (MCM).
Pearson
Correlation and
Hierarchical
regression
443 Fully
registered
clinical and
counselling
psychologists
Coping modes of
detached protector and
detached self‐soother
were most frequently
observed in burnout
psychologists.
6/8
50% of the sample were
Australian. the cross‐sectional
design of this study prevents
attributing causality in the
relationships. The SMI version
used in this study measures only
a small subset of the coping
modes that researchers have
since identified.
#21
To explore factors
contributing to burnout,
specifically, stage of
career.
Consensual
Qualitative
14
Psychologists
Factors related to
burnout included
challenges with tasks
and responsibilities and
10/10
Participants with extremely
distressing experiences or
neutral experiences may not
have responded to the advert.
Well-being and Burnout in Psychologists 31
influence of maladaptive
coping modes, resilience
and job demands on
emotional exhaustion
Principal- 94
components
Psychologists
factor analysis Pearson
correlational
coefficients
Hierarchical
regression
analyses
425
Counselling
and Clinical
Psychologists
80.7% Female
19.03% Male
Psychologists
who 6/8
believe more strongly
that it is unethical to
practice whilst
experiencing burnout
see fewer clients than
psychologists who
believe this less
strongly.
Maladaptive coping 6/8
modes contribute to the
development of burnout
in psychologists.
The sample was skewed due
to self-selection bias; those
who experienced higher burnout
may have chosen not to
participate. Reliability estimate
was relatively low.
A convenience sample of
psychologists. Cross-sectional, no
implications of causality. The
sample size was adequate, but it
may still have been underpowered
to detect interactions.
#22
To investigate the
relationships between
psychologists' beliefs
of burnout and
experience of burnout.
#23
To understand the
Research
methodology
interpersonal
relationships.
Snowballing, so unable to detail
how representative the sample is.
Researchers with a connection to
the participants completed some
coding.

Well-being and Burnout in Psychologists 32
between burnout and type
of work setting, hours of
client contact, years in
present position, and
years employed with
current organisation
Regression
Analysis
Level
Counselling
Psychologists
64% Female
36% Male
practice reported the
lowest levels of burnout.
Psychologists in hospital
settings reported the
highest levels of burnout.
Working more hours a
week was linked to
higher levels of personal
accomplishment. Lower age
is linked to higher burnout.
psychologists who had left the
profession due to burnout. The
gender split is not representative
of national demographics for
psychologists.
#24
To explore the lived
experiences of
psychologists in relation
to burnout
Thematic
Narrative
Enquiry
17
Psychologists.
82.4% Female
17.6 Male
Participants described
high workload/ demands,
lack of job clarity,
autonomy, respect, and
personal difficulties as
factors in their
experience of burnout.
9/10
Didn't capture the experiences of
psychologists who had left the
profession due to burnout. There
was a significant difference in the
average age of the groups; the
burnout group were older.
Cultural theories were not used in
the analysis to explore
sociocultural processes.
#25
To examine relationships
Multiple
521 Doctoral
Psychologists in private
6/8
Didn't capture the experiences of

Well-being and Burnout in Psychologists 33
#26 To investigate sources of Between 93 A high workload was 6/8 Modest sample size. Exploratory stress and burnout in
Group ANOVA Psychologists associated with burnout, cannot describe causality. practising psychologists.
67% Female and burnout was Burnout measure was designed
43% Male associated with for the study and therefore has
decreased professional not been validated. satisfaction.
Quantitative
Qualitative Data
Mixed Methods Study

Well-being and Burnout in Psychologists 34
Quality Summary
All papers were rated as high quality. The lowest scores for qualitative
papers were 7/10 and 6/8 for quantitative papers. Across the included papers,
the risk of bias and limitations were commonly noted concerning the
participants. Several studies only recruited psychologists currently registered
or practising clinically, which means that psychologists who had potentially left
their roles due to burnout were not captured in the data (#5, #8, #14, #16, #17,
#21, #24, #25). A lack of a reflexivity statement from the researchers was a
common quality issue for the qualitative papers (#8, #13), while insufficient
detail regarding the management of confounding variables was noted for
several quantitative papers (#9, #10, #16, #25).
Narrative Synthesis
This review aimed to establish the prevalence, causes and factors
related to burnout in psychologists. The thematic synthesis included the
experiences of 8,256 psychologists. Ten initial quantitative themes and five
qualitative themes emerged from the extracted data (Appendix F). The five
overarching themes are presented below (Figure 3).
Well-being and Burnout in Psychologists 41
Figure 3
Summary of the theme merging process
Individual Analytical Themes Overarching Analytical Themes
Presence of Burnout* Presence of Burnout
Demographic Characteristics*
Age and Gender
Quantitative themes are marked with a *
Qualitative themes are marked with a #
Occupational Experiences*
Support Networks
Personal Resources*
Social Support#
Emotional Intensity and impact of the work#
Professional Culture#
Excessive Job Dema
nds#
Work Setting*
Years’ Experience*
Personal Life#
Humour*
Beliefs about Burnout*
Coping*
Support Network*
Occupational Experiences
Personal Resources
SUBTHEMES: Work Setting, Years’
Experience, Emotional Intensity and
Impact of the work, Professional Culture,
Excessive Job Demands.
SUBTHEMES: Humour, Beliefs about
Burnout, coping, personal life

Well-being and Burnout in Psychologists 37
Theme 1: Presence of Burnout
There was a lack of homogeneity of burnout measures used across the
studies, as shown in Table 5. Except for #14 and #19, all quantitative papers
provided information regarding the burnout rate within their sample. The 91
participants in the qualitative studies all self-reported experiencing burnout; however,
this was a criterion for participation.
Table 5
Burnout Measure Information, Presented Alphabetically.
Burnout Measure Dimensions Measured by Tool No. of Paper IDs Papers
Papers not
reporting
prevalen
c e data
Copenhagen
Burnout Inventory
(CBI)
Personal burnout, work-related
burnout, client-related burnout
4
#5, #6,
#12, #19
#19
Maslach Burnout
Inventory (MBI)
Emotional exhaustion,
depersonalisation, and personal
accomplishment
10
#1, #3, #7,
#11, #15,
#16, #17,
#18, #22,
#25
N/A
Maslach Burnout
Inventory –
Emotional
Exhaustion Scale
Emotional Exhaustion
3
#9, #20,
#23
N/A
Shirom-Melamed
Burnout
Assesses exhaustion across physical,
cognitive, and emotional subscales.
1
#2
N/A

Well-being and Burnout in Psychologists 38
Questionnaire (S
MBQ)
Tedium Burnout Cognitive weariness, fatigue, 1 #10 N/A
Measure (TBM) emotional exhaustion
Job Burnout Enthusiasm toward the job, 1 #14 #14
Syndrome psychological exhaustion, Assessment
indolence, guilt.
Questionnaire
(JBSAQ)
Purpose Four items assessed wellness: two 1 #26 N/A
Designed Burnout addressed burnout, and two
Measure (PDBM) assessed career satisfaction.
The majority of the quantitative papers (#1, #3, #11, #15, #16, #17, #18,
#22, #25) reported average scores for each dimension of burnout compared to
the standardised norms for mental health practitioners, whilst papers #9, #20, and
#23 reported average scores based on general population norms. The remaining
studies reported the number of participants meeting category cut-off scores.
Copenhagen Burnout Inventory. Across the three studies, rates of overall
burnout ranged quite significantly from 8%–30% of the participants; however, for
two studies which reported burnout by category, work-related burnout was
particularly prevalent, with an average of just under 50% (200) of participants
meeting criteria for this (Table 6).
Table 6
Burnout Data from Studies using the CBI.

Well-being and Burnout in Psychologists 39
Paper ID
Levels of Burnout per Dimension
Overall Burnout
#5
Over 35% met the criteria for Personal
Related Burnout.
Over 51% met the criteria for Work-related
burnout.
Less than 15% met the
criteria for overall burnout
#6
Not Reported
8% Met the criteria for
overall burnout
#12
Over 20% met the criteria for Personal
Related Burnout.
Over 42% met the criteria for Work-related
burnout.
30% of participants met
the criteria for overall
burnout
Maslach Burnout Inventory. Though findings around personal
accomplishment and depersonalisation were mixed, participants consistently fell
in either the moderate or high burnout category for emotional exhaustion (Table
7 and figure 4). Only #7 and #25 were limited to one psychological discipline
(clinical and counselling); other papers included Psychologists from a range of
disciplines. The thirteen studies also represented findings encompassing several
countries, including the USA (#1, #9, #11, #16, #17, #18, #20, #22, #23,
#25), Canada (#9, #20), Australia (#7, #9, 20, #23), UK (#9, #20, #23) France
(#3) and Ireland (15). All participants were contacted via their professional
registration body and volunteered to complete online or postal surveys, so
careful consideration of sampling biases weighted towards those with an
invested interest or experience of burnout must be considered alongside findings
relating to prevalence.

Well-being and Burnout in Psychologists 40
Table 7
Burnout Data from Studies Using the MBI Full Scale
Paper
ID
Emotional
Exhaustion
Mean (SD)
Depersonalisation
Mean (SD)
Personal
Accomplishment
Mean (SD)
Level of Burnout using
the standard Norms for
Mental Health
Practitioners
(MBI-MH-S)
#1
19.44 (9.31)
6.31 (4.48)
42.27 (4.52)
EE: Moderate Burnout
DP: Moderate Burnout
PA: Low Burnout
#3
24.50 (8.49)
9.41(3.80)
33.76 (5.13)
EE: High Burnout
DP: High Burnout
PA: Moderate Burnout
#7
Not provided
Not provided
Not provided
Below (Stated by the
researcher)
#11
Not provided
Not provided
Not provided
Low Burnout (Stated by
the researcher)
#15
15.73 (7.5)
3.15 (2.8)
37.62 (4.91)
EE: Moderate Burnout
DP: Low Burnout
PA: Low Burnout
#16
17.75 (9.16)
4.81 (3.76)
41.56 (4.88)
EE: Moderate Burnout
DP: Moderate Burnout
PA: Low Burnout
#17
19.99 (9.83)
5.21 (4.26)
41.64 (4.78)
EE: Moderate Burnout
DP: Moderate Burnout
PA: Low Burnout
#18
16.41 (8.79)
4.42 (3.69)
42.59 (4.45)
EE: Moderate Burnout
DP: Moderate Burnout
PA: Low Burnout
#22
Not provided
Not provided
Not provided
Low Burnout (Stated by
the researcher)
#25
17.83 (8.90)
8.90 (4. 10)
42.09 (4.53)
EE: Moderate Burnout
DP: High Burnout
PA: Low Burnout

Well-being and Burnout in Psychologists 41
Figure 4
Burnout Data from Studies Using the MBI Emotional Exhaustion Scale
90%
80%
70%
60%
50%
40%
30%
20%
10%
0%
SMBQ, TMB, and the Purpose-Designed Questionnaire. 179 of the 828
participants in study #2 scored above the SMBQ cut-off for severe burnout, but
they did not report how many met the criteria for mild-moderate burnout.
The overall level of burnout in study #10 fell in the low-moderate range for the TMB,
with only 14 of the 225 participants in the severe range. 31 of the 93 participants in
study #26 described persistent burnout symptoms on the purpose-designed
questionnaire.
Though there was variation in the overall level of burnout across the
studies, many studies highlighted psychologists experiencing moderate to high
levels of emotional exhaustion, whilst work-related burnout was common amongst
Psychologists completing the CBI.
Moderate Burnout
High Burnout
#9
#20
#23

Well-being and Burnout in Psychologists 42
Theme 2: Age and Gender
Eleven quantitative studies reported findings related to age and gender (Table 8).
Table 8
Findings relating to Burnout, Age and Gender
Paper Burnout Findings Relating to Age Finding Relating to Gender
#25 MBI Age inversely correlated Male Psychologists
reported with EE higher levels of
depersonalisation compared to
female
Younger psychologists report higher levels of EE and may,
ID
Measure
#1
MBI
Younger
Psychologists
experience greater EE
compared to older
colleagues
#6
CBI
Younger
Psychologists
reported higher levels of
burnout
#7
MBI
Higher levels of
EE in women
#16
MBI
Women in agency settings
experience higher EE than
men and women in other
settings
#17
MBI
Women in agency settings
experience higher EE than
men and women in other
settings
#18
MBI
No difference between
burnout in men and women in
agency settings

Well-being and Burnout in Psychologists 43
therefore, be at greater risk of burnout than their older counterparts. This finding
was consistent across studies despite researchers using different burnout
measures and focusing on different burnout dimensions. The studies also covered
a broader range of PPN disciplines, with #1 focused on all
Psychologists with a doctoral qualification, clinical (#6) and counselling (#25)
psychologists; however, the population is limited to North America and Australia.
Results collected using the MBI suggest that women are at a greater risk
of EE than male Psychologists. Women in non-permanent roles, such as
agencies, may be at elevated risk of EE; however, as you can see from table 8,
this finding was inconsistent across studies of participants in the USA (Zippia.,
2023). Notably, 73% of the participants in paper #1 were male. This is three
times higher than North America's national percentage of male psychologists.
Thus, findings may over-represent the experiences of North American male
psychologists. The gender split in all other contributing studies represented their
wider psychological populations.
Theme 3: Occupational Experiences
Subthemes relating to occupational experiences across the qualitative and
quantitative data have overlapping and complementary findings, presented
below.
Work Setting (Quantitative). All the papers used the MBI to measure
burnout; findings are presented in Table 9. Findings suggest that psychologists
working in agency settings and government mental health services may be at greater
risk of burnout than their colleagues in other settings. All studies were conducted with

Well-being and Burnout in Psychologists 44
USA populations, except for #1, which also included Canadian psychologists and #7,
which was conducted with an Australian population.
Table 9
Findings relating to burnout and workplace setting.
Paper ID
Burnout Measure
Finding
#1
MBI
Psychologists in private practice had lower rates of
EE and DP and higher PA than Psychologists in
other settings
#7
MBI
Psychologists in Government mental health
services at an increased risk of EE, DP and PA
#16
MBI
Psychologists working in agencies reported greater
stress and lower levels of PA
#17
MBI
Psychologists working in agencies reported greater
stress and lower levels of PA
#18
MBI
Psychologists working in agencies reported greater
stress and lower levels of PA
#22
MBI
Psychologists in Government mental health
services at an increased risk of EE, DP and PA
#25
MBI
In a comparison of burnout across workplaces:
Psychologists in mental health services have the
highest rates of depersonalisation, private
Psychologists had the lowest rate
Years Experience (Quantitative). This review found evidence that fewer
experienced psychologists experience greater emotional exhaustion and
depersonalisation compared to their more experienced colleagues (#1, #5); however,
Well-being and Burnout in Psychologists 45
no difference in experience was highlighted by paper #10, suggesting a potential role
for inexperience in the role of burnout.
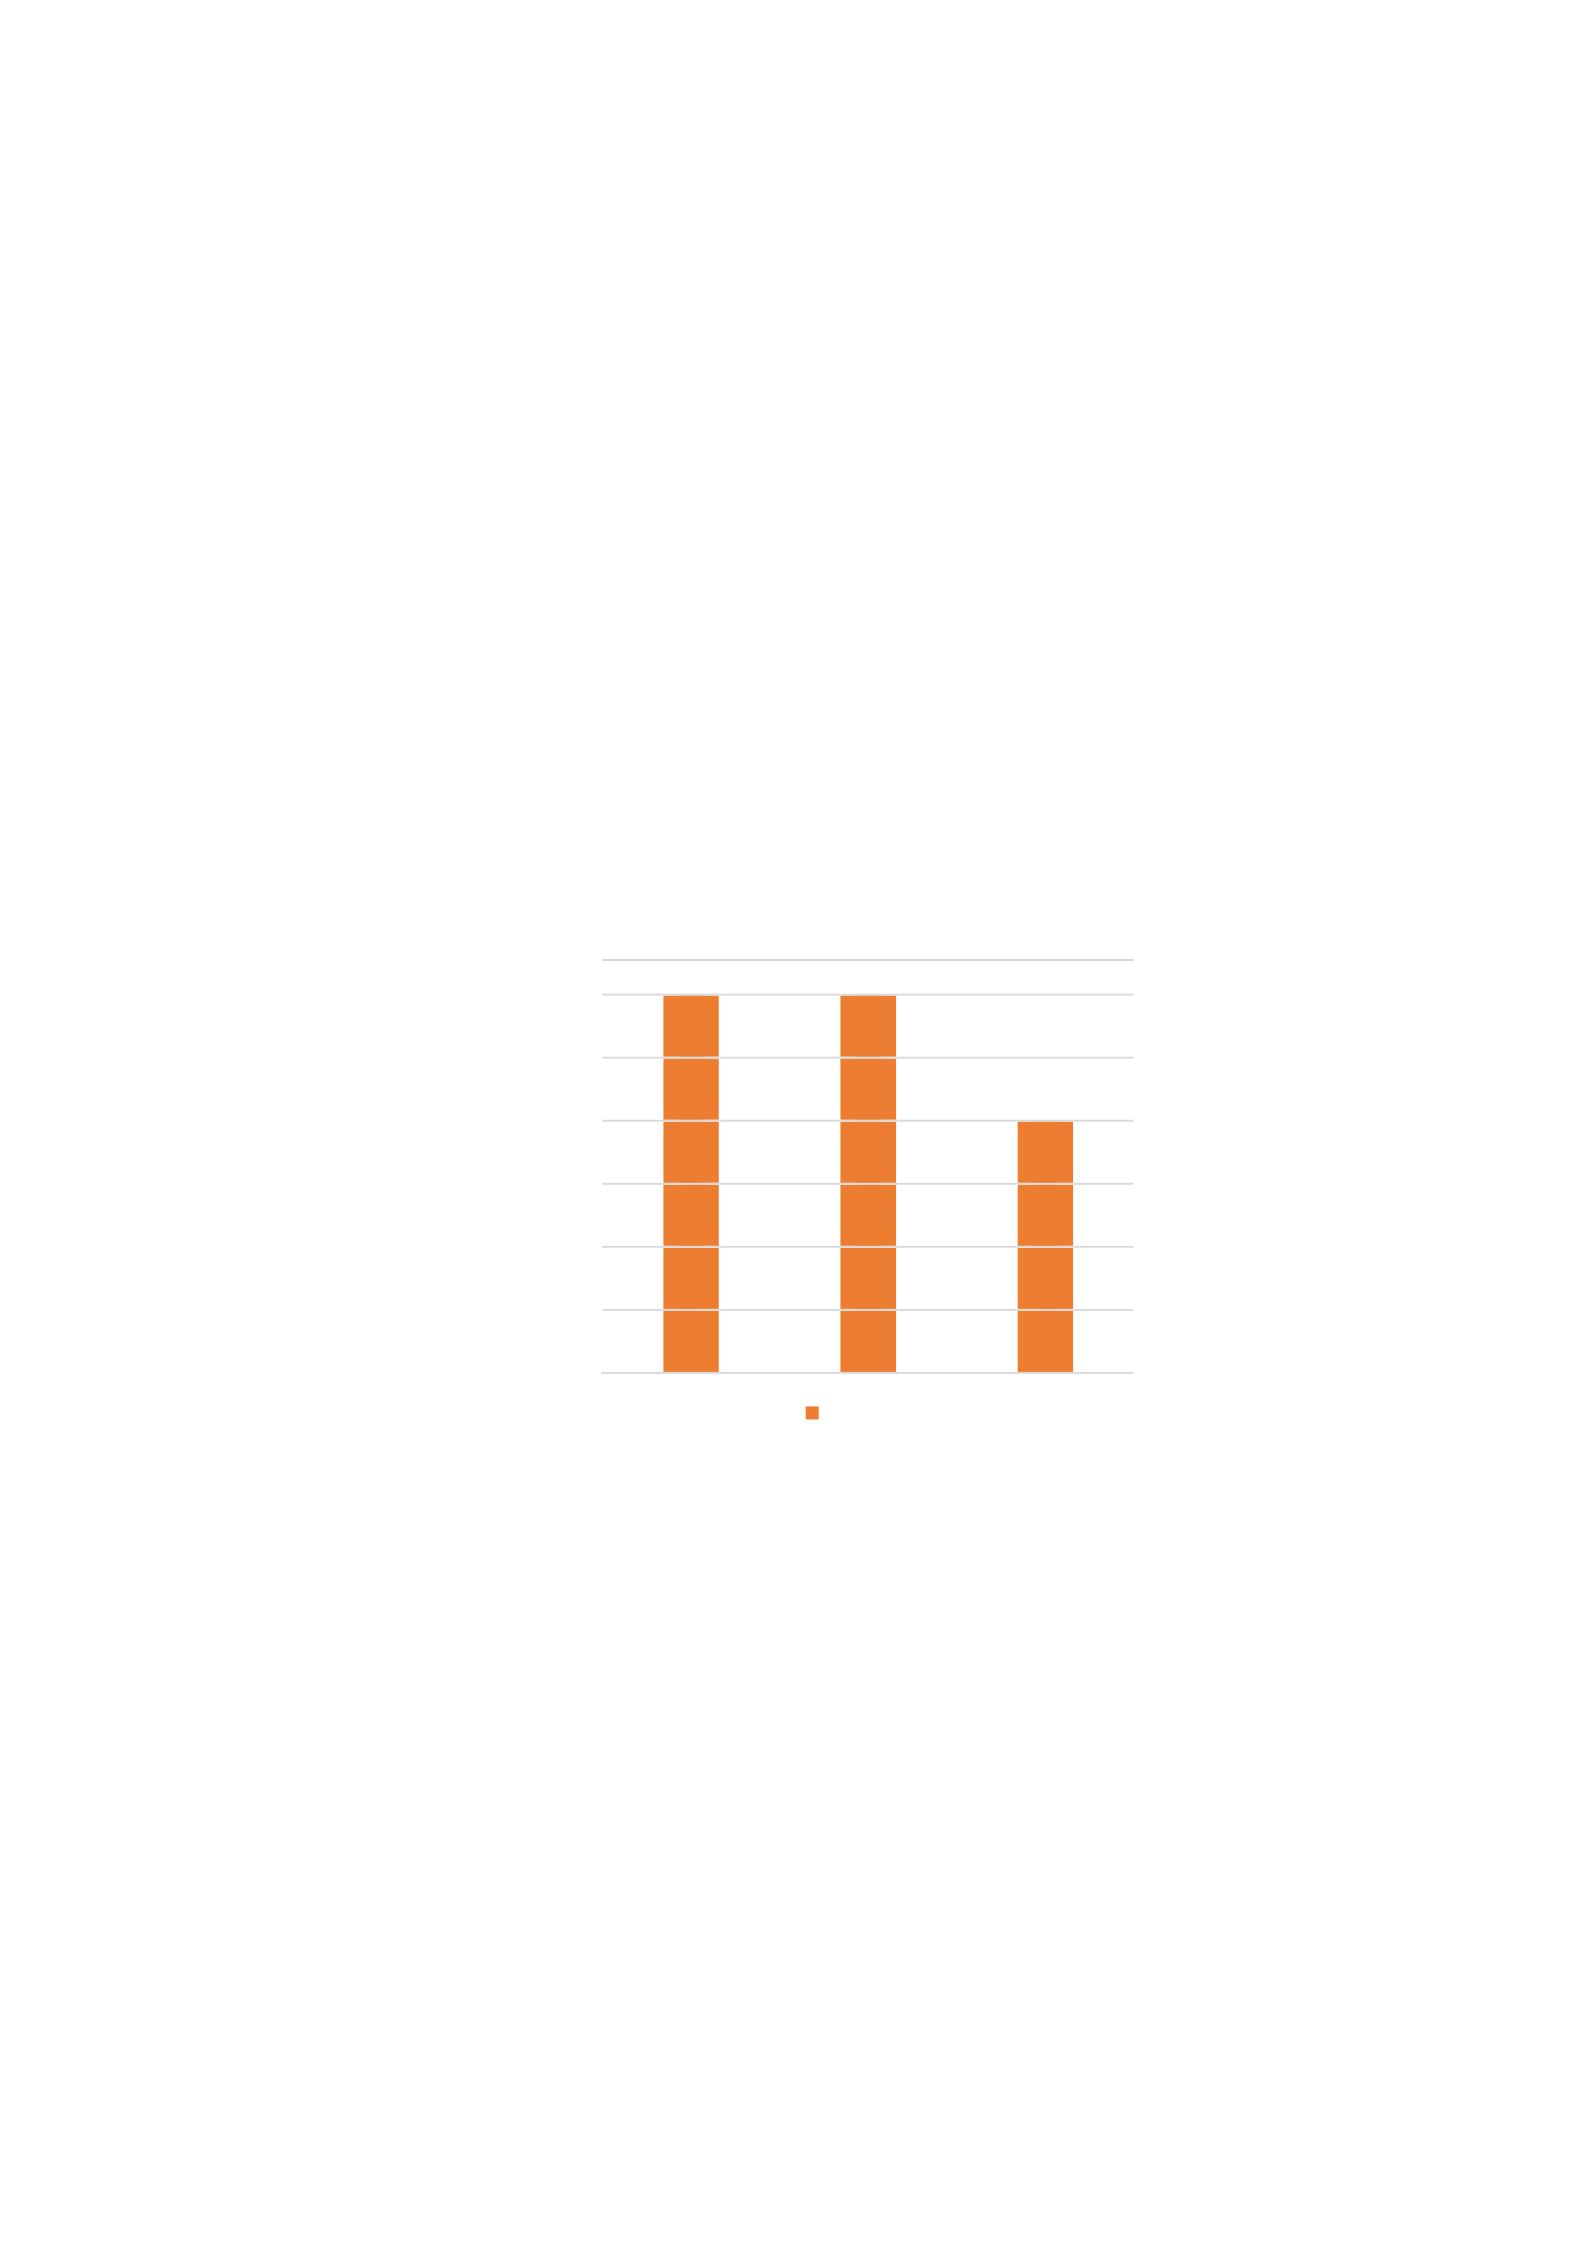
Emotion-Focused Factors (Qualitative and Quantitative). Twelve
papers, six quantitative and six qualitative, highlighted the emotional intensity and
subsequent impact of clinical work as an important factor in Psychologists'
development of burnout (Figure 5).
Figure 5
Graph showing the number of quantitative studies providing evidence for the
relationship between burnout and emotion-focused factors
3.5
3
2.5
2
1.5
1
0.5
0 Conflit Demands
Emotion Focused Coping
Factors
The quantitative data was collected across the MBI, SMBQ, and JDSAQ
and represented several disciplines of Psychologists across Brazil and Ireland, but
primarily North America.
The qualitative data also reflected this theme. Psychologists reported
that high workloads, excessive demands, and insufficient time to complete their
work were all related to burnout. There were several references to psychologists

Well-being and Burnout in Psychologists 46
working over their contracted hours to complete their work on time and
describing their job demands as 'just too much' (Hammond et al., 2018, P.8).
One participant explained the impact of these demands and how it led to their
burnout saying 'I stopped doing things the best I could and just doing things to
get them done’ (McCormack et al., 2015, P.6).
Managing the complex emotions arising from clinical work was a
significant factor in developing burnout.
'what contributes to burnout is seeing clients who really push your
buttons', 'There's that compassion fatigue thing, it's just too much
sometimes'. (Clark et al., 2021, P. 419)
Psychologists' work also appeared to have an impact on their home lives.
Several participants across studies described feeling unable to show their family and
friends the kind of emotional responses that they would like to.
'I'm like a Zombie at the end of the day… I want to have emotion and
show you that, but I've literally got nothing left in the tank'. (Clark et al.,
2021, P. 420)
Professional Culture (Qualitative). Participants across all of the
qualitative studies referred to a lack of discussion and acknowledgement during
their professional training of the risks of burnout in psychologists. One
participant illustrated this by saying, 'They didn't even tell us about burnout…so I
didn't even realise it was something that happened' (Hammond et al., 2018, P.
6).

Well-being and Burnout in Psychologists 47
Similarly, recurrent references were made regarding a lack of discussion about
how to seek support for burnout, with many reporting a stigma around psychologists
asking for help. There were several references to the expectations on psychologists
to 'perform well, be strong, avoid mistakes at all costs, learn from their experiences
and maintain professionalism' (Hammond et al., 2018, p. 6 ). All studies noted that
participants believed the client's needs were more important than their own. This left
many psychologists feeling overwhelmed by their roles and perceived pressure to
perform. Several participants commented on the impact this had on their ability and
willingness to take annual leave, which is captured well by a quote from one
participant who said, 'I felt stressed leading up to my holiday, I felt so guilty about
taking a break from work'.
Theme 4: Personal Resources
Humour (Quantitative). Two studies explored the role of humour in
burnout development, reporting statistically significant relationships. Paper #5
found that maintaining a sense of humour was inversely correlated with overall
levels of burnout, though this association was relatively small. Similarly, paper
#15 explored different types of humour and reported that self-defeating humour
was linked to high emotional exhaustion and depersonalisation levels. There were
some positives associated with humour in this sample. Adaptive forms of humour,
such as affiliative and self-enhancing humour, were highly associated with
personal accomplishment.
Beliefs about Burnout (Quantitative). Only one paper (#23) explicitly
examined participants' beliefs about burnout in relation to their experience. They
found that psychologists who believed more strongly that practising

Well-being and Burnout in Psychologists 48
psychotherapy whilst experiencing burnout was unethical had more knowledge
about preventing burnout and saw fewer clients per week than those who did
not believe it was unethical. They concluded that beliefs about burnout could
impact a person's behaviours at work and, ultimately, their likelihood of
experiencing burnout.
Coping (Quantitative). Amongst the eligible papers, there was a particular
focus on early maladaptive schemas (Bach et al., 2018) and maladaptive coping
modes (MCM)(Simpson et al., 2018) in relation to burnout.
In study #9, the high burnout group reported higher mean scores on all 15
EMSs than the low burnout group. All 15 EMSs significantly predicted
participants' level of burnout more accurately than by chance. Both paper #9
and paper #20 reported that self-sacrifice and unrelenting standards schemas
were the most frequently reported schemas amongst participants with higher
burnout. Paper #20 also reported that all EMSs and MCMs were positively
correlated with emotional exhaustion. Similarly, paper #23 found that each MCM
contributed to predicting participants' levels of emotional exhaustion above the
influence of job demands and resilience.
One paper (#12) explored the relationship between self-compassion and
burnout. Their findings indicated that psychologists with lower levels of
selfcompassion experience higher levels of burnout and more depressive
symptoms. An additional paper (#5) found a strong negative correlation
between the level of burnout and mindfulness, which led them to conclude that
psychologists with fewer mindfulness skills experience higher burnout. This
review suggests that personal factors may play a role in developing burnout.

Well-being and Burnout in Psychologists 49
Several factors were identified, but there were insufficient papers examining
each factor to draw clear conclusions about how important each factor may be.
Personal Life (Qualitative). A clear theme across the six qualitative data
sets related to life outside of participants' work as psychologists, A contributor to
burnout in all groups was personal difficulties and challenges. All the papers
acknowledge that external stressors, personal circumstances or life changes
(such as pregnancy, divorce or transitional ages) were linked to participants'
burnout experiences. One participant summarised the intersection between their
experience of work-related burnout and challenges at home as 'the perfect
storm' (Turnbull & Rhodes., 2021, p. 55).
There is a clear argument that challenges or significant changes in a
person's personal life can impact their risk of developing burnout. It is important
to note that none of the studies collected information on participants' mental
health, which would be a confounding factor in this finding.
Theme 5: Support Networks
Social Support Networks (Quantitative and Qualitative). Three
qualitative papers explored burnout-related social factors, primarily social
support and family-work conflict. Paper #10 found that higher levels of burnout
were associated with less social support, less optimistic expectations, and
higher levels of work-related disillusionment. Regarding work-life balance, higher
work-family conflict was associated with a lower sense of personal
accomplishment, greater emotional exhaustion and depersonalisation of clients.
Three of the core dimensions of burnout, according to the MBI. Discussing work
frustrations with family, friends or colleagues was associated with higher levels

Well-being and Burnout in Psychologists 50
of burnout (paper #5); however, as this study was cross-sectional, it is unclear
whether discussing burnout with others is the cause or effect of burnout.
These findings were complemented by the qualitative findings, which highlighted
the positive significance of the role of the clinical supervisor. Several participants
explained that complicated relationships with supervisors contributed to burnout
as they relied on supervision as a safe and containing space to manage the
difficulties that arose from their work. Without this, the work environment felt
more challenging. Moreover, many spoke of the critical relationship played by
family and friends in managing burnout or avoiding it altogether. This led many
authors to conclude that lacking adequate social support is a risk factor for
developing burnout in psychologists. Interpersonal relationships and the support
networks they provide are important protective factors in psychologists'
experience of burnout.
Cross-Cultural Considerations.
The findings capture the experiences of psychologists working in nine
countries. Their experiences will be impacted by their varied cultural backgrounds,
including different training pathways, healthcare systems and broader socio-
cultural contexts.
Language in Burnout Measures. Cross-cultural considerations may
impact the interpretation of the synthesised data. The conceptualisation of burnout
and the language used to represent and express the concept are particularly
important (Squires et al., 2014). For example, dimensions of the MBI such as
depersonalisation may not exist linguistically or culturally in countries where
English is not the primary language, such as Sweden (#2), Netherlands (#20),

Well-being and Burnout in Psychologists 51
Brazil (#14), France (#3) and the Canadian province of Quebec (#1, #9, #10, #20).
Many of these studies reported using English language outcome measures. This
may impact the rigour of the outcome measure in detecting the prevalence of
burnout across the studies in this review (Maneesriwongul & Dixon., 2004). As
such, the conclusions in this study must be held tentatively and consider the
cross-cultural differences in the language used to define and identify burnout.
Healthcare Systems. There are significant differences in the psychology
and healthcare structures in the USA, Australia and the UK (Papanicolas et al.,
2018), the primary contributors to these themes relating to work settings.
Australia operates a shared public-private system where eligible residents can
access government healthcare free of charge (Duckett & Wilcox., 2015). The
USA has a more complex and primarily private medical system where
government-provided care for eligible individuals is provided at reduced or no
cost (Obama., 2016). On the other hand, the UK has a National Health Service,
free at the point of delivery (Bacon et al., 2022). The difference in how services
are designed, funded and delivered across the study populations will likely
impact the experience of working in a particular professional context. Agency
psychologists in America are likely to experience different stressors than agency
psychologists in Australia, as these agencies provide different services under
varied funding structures. Thus, the term ‘agency’ in this study encompasses a
wide range of working arrangements which differ cross-
culturally.
Psychology Training Pathways. Training pathways vary significantly across
the nine countries. In the UK (Nel et al., 2012) and the USA (Norton et al., 2022),

Well-being and Burnout in Psychologists 52
qualified psychologists usually must complete a doctoral-level qualification. In
Australia, qualified psychologists hold a post-graduate diploma (Norton et al., 2022),
whilst, in Sweden (Allwood et al., 2022) and France (Moser & Rouquette., 2002), an
MSc and proof of experiential learning are accepted for professional registration.
These differences in training experiences are likely to mean that the professional
culture of psychology, the age of newly qualified psychologists and a variety of other
aspects of the experience of psychologists will differ across the countries. Thus
caution must be employed when interpreting these results relating to occupational
experiences, and it must be acknowledged that they represent data from several
distinct professional cultures and not one collective.
Discussion
This systematic review synthesised international data related to the
prevalence, factors and causes of burnout in psychologists. The review findings
suggest that psychologists across North America and Europe may experience
moderate to high levels of emotional exhaustion compared to standard norms for
mental health practitioners. Age, gender and years of experience were all found
to be important factors in the development of burnout. Occupational
experiences, such as job demands and personal resources, such as ways of
coping, also appeared to play an important role. Positive support networks were
critical in minimising psychologists' experience of burnout. Findings are
discussed in the context of existing research and the potential clinical
implications.
Findings suggest that psychologists may experience higher levels of emotional
exhaustion than their mental health colleagues. Given that psychologists often work

Well-being and Burnout in Psychologists 53
with clients experiencing high levels of, this finding is not unsurprising (Rupert &
Dorociak., 2019). Although, some researchers argue that the emotional exhaustion
scale of the MBI is the only sub-scale sensitive enough to capture burnout and, as
such, may account for the higher levels of emotional exhaustion compared to
depersonalisation and personal accomplishment (Smout et al., 2022). Reliably
integrating findings from studies using different outcome measures was a significant
challenge in this review as the dimensions of burnout being measured differ too
significantly to compare,
e.g. emotional exhaustion compared with personal, professional, and workrelated
burnout. As a result, findings are based on just 13 of the total 26 studies which
reported burnout in their samples and must be held tentatively.
None of the eligible studies examined the national prevalence of
psychologist burnout in the UK. Accessible and reliable prevalence data is
essential in understanding the progression of conditions within a population and
planning appropriate, targeted and effective intervention strategies (Fairchild et al.,
2018). The absence of published, peer-reviewed, national prevalence data may
hinder the development of appropriate strategies for preventing and supporting
psychologists experiencing burnout (Ben-Zur & Michael, 2007; BPS, 2020). Future
research may benefit from capturing prevalence data in the UK as an essential
step towards understanding and preventing burnout risk in psychologists in the UK
healthcare workforce.
In other healthcare roles, such as GPs (Abdulla et al., 2011), doctors
(Amoafo et al., 2015), and nurses (Gómez‐Urquiza et al., 2017; MembriveJiménez
et al., 2020) younger professionals are at a greater risk of burnout than their older

Well-being and Burnout in Psychologists 54
counterparts. Our findings were consistent with these reviews. As many eligible
studies were cross-sectional, we cannot explain causation; however, we can use
the Job Demands-Resources Model (Bakker & Demerouti., 2007) to offer one
hypothesis for these findings. Younger psychologists may be more likely to be
experiencing life transitions, which may place greater demands on their resources
(Blair., 2000). Some transitional stages may disproportionately affect females,
particularly childcare responsibilities accounting somewhat for the gender
differences our review observed. Though results were more mixed, female
psychologists, much like their other multidisciplinary colleagues (Hoff & Lee.,
2021), appear at greater risk for burnout than their male colleagues. Psychologists
across the western world work in a wide variety of different settings. Whilst this
review found evidence for the role of age and gender in psychological burnout, it
requires a more nuanced investigation. For example, findings were reported in
binary gender categories, not capturing the experience of the increasing number of
psychologists who identify as non-binary (Richards & Barrett., 2020). Future
research could aim to explore less binary concepts of gender and interactions
between these factors and others, such as age and workplace.
Many of the occupational factors linked to higher levels of burnout in
psychologists were consistent with the research relating to other healthcare
professionals, particularly high workloads, long hours, lacking resources and high
demand (Amoafo et al ., 2015; O'Connor et al., 2018 Patel et al., 2018). Two
subthemes appeared to be more specific to psychologists; professional culture
and the emotional intensity and impact of the work.
Psychology is a highly competitive field. From gaining pre-training experience
securing a place on a training programme (Scior et al., 2014;

Well-being and Burnout in Psychologists 55
Callahan et al., 2018 ), completing rigorous training academic requirements
(Pakenham & Stafford‐Brown, 2012) and working in complex systems
(Kannampallil et al., 2011), psychologists experience pressure throughout their
professional journeys (Cushway and Tyler., 1996). The stressors are well
documented. Given this picture of the psychology field as highly ambitious and
competitive (Ragavan., 2018), it is unsurprising that this review found that
perceived and experienced pressure was a significant factor in psychologists'
experience of burnout. There was also a clear link between engaging with clients
with high levels of distress and higher levels of burnout, with a particular focus
on the negative impact this had on psychologists' ability to manage personal
relationships at home.
These findings suggest that for some psychologists, the very nature of
their work can be a significant risk factor in the development of burnout. As
such, interventions and strategies for burnout prevention could benefit from
more systemic approaches, targeting the psychology profession and
organisations which employ them (Zinsstag et al., 2011). Research tends to
focus on exploring the negative impacts of working with high levels of distress,
such as burnout; however (Sodeke-Gregson et al ., 2013), we must be careful to
acknowledge that, as evidenced by our findings, not all psychologists
experience burnout. Exploring the experience of psychologists who experience
positive work-related well-being could allow researchers to consider what we
can learn from psychologists who are not experiencing burnout. This exploration
could be beneficial in understanding how to best support the workforce's needs.
Review findings supported evidence demonstrating a multidirectional
relationship between burnout and personal experiences (Asanta et al., 2019; De

Well-being and Burnout in Psychologists 56
Hert., 2020), with one participant referring to the interaction as 'the perfect
storm' (Turnbull & Rhodes., 2021, p. 55). Use of humour, beliefs about ethical
practice, and mindfulness were all suggested to be linked to burnout levels;
however, there was not enough data to provide conclusive links in this review.
Far more exploration of these is required to understand their role in developing
burnout.
Social support appears to have positive and negative impacts on
psychologists' experience of burnout. Interpersonal relationships have long been
acknowledged as important sources of social support that can promote
healthcare staff's well-being and mental health (Stubbs & Achat., 2022).
Psychologists perceived positive interpersonal relationships with supervisors as
a mediating factor in developing burnout. Other healthcare professionals have
reported similar findings (Dyrbye & Shanafelt, 2016; Ruisoto. 2021). Much like
their healthcare colleagues, psychologists highlighted interpersonal conflict, with
family, and workplace supervisors, as negatively contributing to their experience
of well-being at work (Lloyd et al., 2002). This is an important finding as
supervision is positioned as a tool to ensure the efficacy and safety of
psychologists' work and safeguard their emotional well-being (Falender, 2018).
Ensuring that high-quality supervision is available for psychologists should be a
priority for employers. However, caution must be given to supervision limitations
as effective prevention, as evidence suggests supervisory experiences improve
disengagement but do not reduce emotional exhaustion (Johnson et al., 2021).
Thus, an integrative approach to burnout, encompassing a range of support, is
likely to be required.

Well-being and Burnout in Psychologists 57
Expansion of Knowledge Base and Clinical Implications
In line with McCormack et al.’s (2018) findings concerning allied
psychological professions, this review suggests that emotional exhaustion is
salient in the experience of burnout for trainee and qualified psychologists. To
the researcher's knowledge, it is the first review to report findings related
explicitly to burnout in this population. By focusing on professional
psychologists, the researchers have identified profession-specific experiences,
such as the emotional intensity of their work and the culture in the psychology
profession, which may contribute to emotional exhaustion in psychologists. This
enables the researcher to make profession-specific recommendations to support
the needs of professional psychologists.
Given that there are arguments for both individual responsibility (West et
al., 2018) and corporate social responsibility (Liu et al., 2023) in preventing and
managing employee burnout, findings indicate that psychologists and those who
employ psychologists may benefit from attending to early signs of fatigue,
apathy and emotional disengagement. Interventions for emotional exhaustion in
front-line healthcare staff should focus on identifying causation factors and
supporting the reduction of symptoms (McFarland & Hlubocky., 2021).
Employers and individuals may wish to consider mindfulness-based
interventions, which have positively impacted emotional exhaustion in the
general workplace population (Hülsheger et al., 2013) and specifically with
healthcare staff (Kriakous et al., 2021).
Findings also suggest that younger and less experienced psychologists may
be at an increased risk for developing burnout. Therefore, it may benefit

Well-being and Burnout in Psychologists 58
psychologists and employers to increase support for and monitoring of
psychologists’ emotional well-being in the pre-qualification and newly qualified
stages. This could be achieved through increased frequency of supervision,
supportive peer spaces for newly qualified psychologists and clear and accessible
pathways for supporting well-being.
Interpersonal conflict and team dynamics may also contribute to
psychologists’ experience of burnout. We must consider this in light of the
knowledge that psychologists are often positioned to mediate team conflict via
reflective practice (Heneghan et al., 2014), which may become an interpersonal
workplace stressor. Again, research exploring the impact of team dynamics
specifically on psychologists would be of benefit; however, employers could
consider outsourcing reflective practice spaces from psychologists outside of their
team to help minimise the emotional impact of this role.
Limitations and Future Research
Grey literature was excluded to support the rigour of the review; however,
many psychologists in training conduct research regarding psychologists'
experience with burnout but do not go on to publish their findings. Future
reviews may wish to include grey literature and adopt a rigorous quality
assessment process to exclude papers of insufficient quality before analysis,
widening the potential pool of eligible studies.
Consideration must be given to the integrated approach to the narrative
synthesis. The researchers followed JBI's advice to qualitise the quantitative data
as codifying quantitative data produces fewer errors than attributing numerating
qualitative data (Stern et al., 2020). Despite this, researchers acknowledge that

Well-being and Burnout in Psychologists 59
qualitising data is a relatively under-researched area and rely heavily on the
researchers' ability to consistently apply their research principles to the
conversion process, which will likely impact the data analysis and interpretation
(Dixon-Woods et al., 2005). Additionally, the findings are based only on the data
reported by the authors of the included papers (Aveyard., 2018). For the findings
drawn from qualitative studies, the researcher's beliefs about the data and
phenomenon of interest will have impacted the interpretation of the findings
(Smith et al., 2021).
Despite many burnout measures having satisfactory validity and reliability
(Kristensen et al., 2005), different tools are likely to report varying levels of
burnout depending on the dimensions they measure. The lack of homogeneity
of burnout measures in this review means that caution must be employed when
considering generalising the findings of this review across populations, settings,
and countries. Future reviews into burnout research may benefit from
considering the most widely used burnout tool in research and clinical settings in
their country of origin to support the generalisability of findings. This could be
incorporated into their inclusion and exclusion criteria.
Conclusion
This review was the first to explore the prevalence and factors related to
burnout in qualified psychologists. Several factors are associated with the
development of burnout, many of which are consistent with burnout for their
healthcare colleagues; psychologists may experience additional risk factors due
to the emotional intensity and impact of their work and the culture of the
psychology profession. Psychologists may experience moderate to high levels

Well-being and Burnout in Psychologists 60
of emotional exhaustion burnout linked to their occupation; however, providing
an accurate overall prevalence is challenging due to vast differences in how
prevalence data is collected and reported.
References

Well-being and Burnout in Psychologists 61
Abdulla, L., Al-Qahtani, D. M., & Al-Kuwari, M. G. (2011). Prevalence and
determinants of burnout syndrome among primary healthcare physicians in
Qatar. South African Family Practice, 53(4), 380-383.
https://doi.org/10.1080/20786204.2011.10874118
Ackerley, G. D., Burnell, J., Holder, D. C., & Kurdek, L. A. (1988). Burnout
among licensed psychologists. Professional Psychology: Research and
Practice, 19(6), 624-629. https://doi.org/10.1037/0735-7028.19.6.624 Allwood,
C. M., Geisler, M., & Buratti, S. (2022). The relationship between personality,
work, and personal factors to burnout among clinical psychologists: exploring
gender differences in Sweden. Counselling
Psychology Quarterly, 35(2), 323 -343.
https://doi.org/10.1080/09515070.2020.1768050
Amoafo, E., Hanbali, N., Patel, A., & Singh, P. (2015). What are the significant
factors associated with burnout in doctors? Occupational Medicine,
65(2), 117-121. https://doi.org/10.1080/09515070.2020.1768050
Asante, J. O., Li, M. J., Liao, J., Huang, Y. X., & Hao, Y. T. (2019). The
Relationship between psychosocial risk factors, burnout and quality of life
among primary healthcare workers in rural Guangdong Province: a cross
sectional study. BMC Health Services Research, 19(1), 1-10.
https://doi.org/10.1186/s12913
Aveyard, H. (2018). Doing a literature review in health and social care: A
practical guide. McGraw-Hill
Azoulay, E., De Waele, J., Ferrer, R., Staudinger, T., Borkowska, M., Povoa, P.,

Well-being and Burnout in Psychologists 62
Lliopoulou, K., Artigas, A., Schaller, S., Shankur Hari, M., Pellegrini, M.,
Darmon, M., Kesecioglu, J., & Cecconi, M. (2020). Symptoms of burnout in
intensive care unit specialists facing the COVID-19 outbreak. Annals of
Intensive Care, 10(1), 1-8. https://doi.org/10.1186/s13613-020-00722-3
Bacon, A., Martin, E., Swarbrick, R., & Treadgold, A. (2022). National health
service interventions in England to improve care to armed forces veterans.
BMJ Mil Health, 168(1), 95-98. http://dx.doi.org/10.1136/bmjmilitary-2020-
001739
Bakker, A. B., & Demerouti, E. (2007). The job demands‐resources model:
State of the art. Journal of Managerial Psychology, 22(3), 309-328.
https://doi.org/10.1108/02683940710733115
Ben-Zur, H., & Michael, K. (2007). Burnout, social support, and coping at work
among social workers, psychologists, and nurses: The role of challenge
/ control appraisals. Social Work in Health Care, 45(4), 63-82.
https://doi.org/10.1300/J010v45n04_04
Berjot, S., Altintas, E., Grebot, E., & Lesage, F. X. (2017). Burnout risk profiles
among French psychologists. Burnout Research, 7, 10-20.
https://doi.org/10.1016/j.burn.2017.10.001
Blair, S. E. (2000). The centrality of occupation during life transitions. British
Journal of Occupational Therapy, 63(5), 231-237.
Boland A, Cherry M, Dickson R. Doing a systematic review: a student’s
guide. Sage.

Well-being and Burnout in Psychologists 63
Bridgeman, P. J., Bridgeman, M. B., & Barone, J. (2018). Burnout syndrome
Among healthcare professionals. The Bulletin of the American Society of
Hospital Pharmacists, 75(3), 147-152.
https://doi.org/10.2146/ajhp170460
British Psychological Society (2017) Practice guidelines: Third edition.
https://tinyurl.com/mt6mkzem
British Psychological Society (2019) Standards for the accreditation of Doctoral
programmes in clinical psychology. https://tinyurl.com/ycxtut4t
Callahan, J. L., Smotherman, J. M., Dziurzynski, K. E., Love, P. K., Kilmer, E.
D., Niemann, Y. F., & Ruggero, C. J. (2018). Diversity in the professional
psychology training-to workforce pipeline: Results from doctoral psychology
student population data. Training and Education in
Professional Psychology, 12(4), 273- 285.
https://doi.org/10.1037/tep0000203
Cavanagh, N., Cockett, G., Heinrich, C., Doig, L., Fiest, K., Guichon, J. R.,
Page, S., Mitchel, I., & Doig, C. J. (2020). Compassion fatigue in healthcare
providers: A systematic review and meta-analysis.
Nursing Ethics, 27(3), 639-665.
https://doi.org/10.1177/096973301988940
Channer, K., Onionaiye, M., Williams, D., & Mason, B. (2018) Exploring the
leadership competencies of trainee clinical psychologists and qualified
clinical psychologists. https://tinyurl.com/ycx6jfw8

Well-being and Burnout in Psychologists 64
Clarke, J. J., Rees, C. S., Breen, L. J., & Heritage, B. (2021). The perceived
effects of emotional labor in psychologists providing individual
psychotherapy. Psychotherapy, 58(3), 414- 424.
https://doi.org/10.1037/pst0000351
Cooke, A., Smith, D., & Booth, A. (2012). Beyond PICO: the SPIDER tool for
Qualitative evidence synthesis. Qualitative Health Research, 22(10),
1435-1443. https://doi.org/10.1177/1049732312452938
Cosgrave, C. (2020). The whole-of-person retention improvement framework: a
guide for addressing health workforce challenges in the rural context.
International Journal of Environmental Research and Public Health,
17(8). https://www.mdpi.com/1660-4601/17/8/2698
Cushway, D., & Tyler, P. (1996). Stress in clinical psychologists. International
Journal of Social Psychiatry, 42(2), 141-149.
De Hert, S. (2020) Burnout in Healthcare Workers: Prevalence, Impact and
Preventative Strategies. Local and Regional Anesthesia, 13, 171-183.
Di Benedetto, M., & Swadling, M. (2014). Burnout in Australian psychologists:
Correlations with work-setting, mindfulness and self-care behaviours.
Psychology, Health & Medicine, 19(6), 705-715.
https://doi.org. 10.1080/13548506.2013.861602
Dixon-Woods, M., Agarwal, S., Jones, D., Young, B., & Sutton, A. (2005).
Synthesising qualitative and quantitative evidence: a review of possible methods.
Journal of Health Services Research & Policy, 10(1), 45-53.
https://doi/pdf/10.1177/135581960501000110

Well-being and Burnout in Psychologists 65
Dolan, E. D., Mohr, D., Lempa, M., Joos, S., Fihn, S. D., Nelson, K. M., &
Helfrich, C. D. (2015). Using a single item to measure burnout in primary care
staff: a psychometric evaluation. Journal of General Internal
Medicine, 30, 582-587. https://doi.org/10.1007/s11606-014-3112-6
D'souza, F., Egan, S. J., & Rees, C. S. (2011). The relationship between
perfectionism, stress and burnout in clinical psychologists. Behaviour Change,
28(1), 17-28.
Duckett, S., & Willcox, S. (2015). The Australian health care system.
Oxford University Press.
Dyrbye, L., & Shanafelt, T. (2016). A narrative review on burnout experienced
by medical students and residents. Medical Education, 50(1), 132-149.
https://doi.org/10.1111/medu.12927
Dyrbye, L. N., Thomas, M. R., Massie, F. S., Power, D. V., Eacker, A., Harper,
W., Durning, S., Moutier, C., Szydlo, D.W., Novotny, P.J., Sloan, J.., &
Shanafelt, T. D. (2008). Burnout and suicidal ideation among US medical
students. Annals of Internal Medicine, 149(5), 334-341.
https://doi.org/10.7326/0003-4819-149-5-200809020-00008
Edú-Valsania, S., Laguía, A., & Moriano, J. A. (2022). Burnout: A review of
theory and measurement. International Journal of Environmental
Research and Public Health, 19(3), 1780-1793.
https://doi.org/10.3390/ijerph19031780
Emery, S., Wade, T. D., & McLean, S. (2009). Associations among therapist
beliefs, personal resources and burnout in clinical psychologists.

Well-being and Burnout in Psychologists 66
Behaviour Change, 26(2), 83-96. https://doi.org/10.1375/bech.26.2.83 Etkind,
S. N., Bone, A. E., Lovell, N., Higginson, I. J., & Murtagh, F. E. (2018). Influences
on care preferences of older people with advanced illness: a systematic review
and thematic synthesis. Journal of the American
Geriatrics Society, 66(5), 1031-1039. https://doi.org/10.1111/jgs.15272
Fairchild, G., Tasseff, B., Khalsa, H., Generous, N., Daughton, A. R., Velappan,
N., Priedhorsky, R., & Deshpande, A. (2018). Epidemiological data
challenges: planning for a more robust future through data standards.
Frontiers in Public Health, 6, 336 -344.
https://doi.org/10.3389/fpubh.2018.00336
Falender, C. A. (2018). Clinical supervision—the missing ingredient. American
Psychologist, 73(9), 1240- 1250. https://doi.org/10.1037/amp0000385
Freudenberger, H. J. (1974). Staff burn‐out. Journal of Social Issues, 30(1),
159-165. https://doi.org/10.1111/j.1540-4560.1974.tb00706.x
Fukui, S., Wu, W., & Salyers, M. P. (2019). Impact of supervisory support on
turnover intention: The mediating role of burnout and job satisfaction in a
longitudinal study. Administration and Policy in Mental Health and
Mental Health Services Research, 46(4), 488-497.
https://doi.org/10.1007/s10488-019-00927-0.
Gómez‐Urquiza, J. L., Vargas, C., De la Fuente, E. I., Fernández‐Castillo, R., &
Cañadas‐De la Fuente, G. A. (2017). Age as a risk factor for burnout syndrome
in nursing professionals: a meta‐analytic study. Research in Nursing & Health,
40(2), 99-110.https://doi.org/10.1002/nur.21774 Gonda, X., & Tarazi, F. I. (2022). Well-

Well-being and Burnout in Psychologists 67
being, resilience and post-traumatic growth in the era of Covid-19 pandemic.
European Neuropsychopharmacology, 54(1), 65-66.
https://do.org/10.1016/j.euroneuro.2021.08.266
Gorgievski, M. J., & Hobfoll, S. E. (2008). Work can burn us out or fire us up:
Conservation of resources in burnout and engagement. In J. R. B.
Halbesleben (Eds.), Handbook of stress and burnout in health care (pp.
7-22). Nova Science. https://tinyurl.com/42t6h82c
Guidroz, A. M., Wang, M., & Perez, L. M. (2012). Developing a model of source
Specific interpersonal conflict in health care. Stress and Health, 28(1),
69-79. https://doi.org/10.1002/smi.1405
Hall, L. H., Johnson, J., Watt, I., Tsipa, A., & O’Connor, D. B. (2016). Healthcare
Staff wellbeing, burnout, and patient safety: a systematic review. PloS
One, 11(7). https://journals.plos.org/plosone/article/file?id=10.1371/
journal.pone.0159015&type=printable
Hammond, T. E., Crowther, A., & Drummond, S. (2018). A thematic inquiry into
the burnout experience of Australian solo-practicing clinical psychologists.
Frontiers in Psychology, 8(1996), 1-13.
https://doi.org/10.3389/fpsyg.2017.01996
Heneghan, C., Wright, J., & Watson, G. (2014). Clinical psychologists'
experiences of reflective staff groups in inpatient psychiatric settings: A mixed
methods study. Clinical Psychology & Psychotherapy, 21(4), 324
340. https://doi.org/10.1002/cpp.1834
Higher Education England. (2021). Psychological Professions Workforce Plan
for England. https://tinyurl.com/2hnxefku

Well-being and Burnout in Psychologists 68
Hoff, T., & Lee, D. R. (2021). Burnout and Physician Gender: What Do We
Know? Medical Care, 59(8), 711-720.
https://doi.org/10.1097/MLR.0000000000001584
Hong, Q. N., Gonzalez‐Reyes, A., & Pluye, P. (2018). Improving the usefulness
of a tool for appraising the quality of qualitative, quantitative and mixed
methods studies, the Mixed Methods Appraisal Tool (MMAT). Journal of
Evaluation in Clinical Practice, 24(3), 459-467.
https://doi.org/10.1111/jep.1288
Hülsheger, U. R., Alberts, H. J., Feinholdt, A., & Lang, J. W. (2013). Benefits of
mindfulness at work: the role of mindfulness in emotion regulation,
emotional exhaustion, and job satisfaction. Journal of Applied
Psychology, 98(2), 310- 325. https://doi.org/10.1037/a0031313
Iqbal, Z., Airey, N. D., Brown, S. R., Wright, N. M., Miklova, D., Nielsen, V.,
Webb., K & Sajjad, A. (2021). Waiting list eradication in secondary care
psychology: Addressing a National Health Service blind spot. Clinical
Psychology & Psychotherapy, 28(4),
969-977. https://doi.org/10.1002/cpp.2551
Joanna Briggs Institute. (2017). Checklist for systematic reviews and research
syntheses. https://joannabriggs.org/ebp/critical_appraisal_tools
Johnson, J., Corker, C., & O'connor, D. B. (2020). Burnout in psychological
therapists: A cross‐sectional study investigating the role of supervisory
relationship quality. Clinical Psychologist, 24(3), 223-235.
https://doi.org/10.1111/cp.12206

Well-being and Burnout in Psychologists 69
Johnson, J., Hall, L. H., Berzins, K., Baker, J., Melling, K., & Thompson, C.
(2018). Mental healthcare staff well‐being and burnout: A narrative
review of trends, causes, implications, and recommendations for future
interventions. International Journal of Mental Health Nursing, 27(1), 20
32. https://doi.org/10.1111/inm.12416
Johnson, S., Osborn, D. P., Araya, R., Wearn, E., Paul, M., Stafford, M.,
Wellman, N., Nolan, F., Killaspy, H., Lloyd-Evans, B., Anderson, E., &
Wood, S.J., (2012). Morale in the English mental health workforce:
questionnaire survey. The British Journal of Psychiatry, 201(3), 239-246.
https://doi.org/10.1192/bjp.bp.111.098970.
Kaeding, A., Sougleris, C., Reid, C., van Vreeswijk, M. F., Hayes, C., Dorrian,
J., & Simpson, S. (2017). Professional burnout, early maladaptive
schemas, and physical health in clinical and counselling psychology
trainees. Journal of Clinical Psychology, 73(12), 1782-1796.
https://doi.org/10.1002/jclp.22485
Kahill, S. (1986). Relationship of burnout among professional psychologists to
Professional expectations and social support. Psychological Reports,
59(3), 1043-1051. https://doi.org/10.2466/pr0.1986.59.3.1043
Kannampallil, T. G., Schauer, G. F., Cohen, T., & Patel, V. L. (2011).
Considering complexity in healthcare systems. Journal of Biomedical
Informatics, 44(6), 943-947. https://doi.org/10.1016/j.jbi.2011.06.006 Kirby, R.
(2023). Dealing with the NHS staff recruitment and retention crisis: how are
we doing?. Trends in Urology & Men's Health, 14(1), 28-30.
https://doi.org/10.1002/tre.892

Well-being and Burnout in Psychologists 70
Kowalewski, K., McLennan, J. D., & McGrath, P. J. (2011). A preliminary
investigation of wait times for child and adolescent mental health services in
Canada. Journal of the Canadian Academy of Child and Adolescent
Psychiatry, 20(2), 112-119.
Kriakous, S. A., Elliott, K. A., Lamers, C., & Owen, R. (2021). The effectiveness
of mindfulness-based stress reduction on the psychological functioning of
healthcare professionals: A systematic review. Mindfulness, 12, 1-28.
https://doi.org/10.1007/s12671-020-01500-9
Kristensen, T. S., Borritz, M., Villadsen, E., & Christensen, K. B. (2005). The
Copenhagen Burnout Inventory: A new tool for the assessment of burnout.
Work & Stress, 19(3), 192-207 https://doi.org/10.1080/02678370500297720
Kumary, A., & Baker, M. (2008). Stresses reported by UK trainee counselling
psychologists. Counselling Psychology Quarterly, 21(1), 19-28.
https://doi.org/10.1080/09515070801895626
Liu, Y., Cherian, J., Ahmad, N., Han, H., de Vicente-Lama, M., & Ariza-Montes,
A. (2023). Internal corporate social responsibility and employee burnout: an
employee management perspective from the healthcare sector.
Psychology Research and Behavior Management, 16(2023), 283-302.
Lloyd, C., King, R., & Chenoweth, L. (2002). Social work, stress and burnout: A
review. Journal of Mental Health, 11(3), 255-265.
https://doi.org/10.1080/09638230020023642
Malinowski, A. J. (2013). Characteristics of job burnout and humor among
psychotherapists. Humor, 26(1), 117-133. https://doi.org/10.1515/humor

Well-being and Burnout in Psychologists 71
2013-0007
Maneesriwongul, W., & Dixon, J. K. (2004). Instrument translation process: a
methods review. Journal of Advanced Nursing, 48(2), 175-186.
https://doi.org/10.1111/j.1365-2648.2004.03185.x
Maslach, C., & Jackson, S. E. (1981). The measurement of experienced
burnout. Journal of Organizational Behavior, 2(2), 99-113.
https://doi.org/10.1002/job.4030020205
Maslach, C., Jackson, S. E., & Leiter, M. P. (1997). Maslach burnout inventory.
Scarecrow Education.
Maslach, C., & Leiter, M. P. (2008). Early predictors of job burnout and
engagement. Journal of Applied Psychology, 93(3), 498-512.
https://doi.org/10.1037/0021-9010.93.3.498
Maslach, C., Schaufeli, W. B., & Leiter, M. P. (2001). Job burnout. Annual
Review of Psychology, 52(1), 397-422.
https://doi.org/10.1146/annurev.psych.52.1.397
McCade, D., Frewen, A., & Fassnacht, D. B. (2021). Burnout and depression in
Australian psychologists: The moderating role of self-compassion.
Australian Psychologist, 56(2), 111-122.
https://doi.org/10.1080/00050067.2021.1890979
McCormack, H. M., MacIntyre, T. E., O’Shea, D., Campbell, M. J., & Igou, E. R.
(2015). Practicing what we preach: Investigating the role of social support in
sport psychologists’ well-being. Frontiers in

Well-being and Burnout in Psychologists 72
Psychology, 6(1854).
https://www.frontiersin.org/articles/10.3389/fpsyg.2015.01854/full
McCormack, H. M., MacIntyre, T. E., O'Shea, D., Herring, M. P., & Campbell, M.
J. (2018). The prevalence and cause (s) of burnout among applied
psychologists: A systematic review. Frontiers in Psychology, 9(1897).
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6198075/
McFarland, D. C., & Hlubocky, F. (2021). Therapeutic strategies to tackle
burnout and emotional exhaustion in frontline medical staff: Narrative
review. Psychology Research and Behavior Management, 14(1) 1429
1436.
Membrive-Jiménez, M. J., Pradas-Hernández, L., Suleiman-Martos, N., Vargas
Román, K., Cañadas-De la Fuente, G. A., Gomez-Urquiza, J. L., & De la
Fuente-Solana, E. I. (2020). Burnout in nursing managers: a systematic
review and meta-analysis of related factors, levels and prevalence.
International Journal of Environmental Research and Public Health,
17(11), 3983-3990. https://doi.org/10.3390/ijerph17113983
Millar, H. L. (2019). The UK NHS Experience of Burnout: Time for Action.
International Journal of Person-Centered Medicine, 9(3), 7-18.
https://doi.org/10.5750/ijpcm.v9i3.994
Morse, G., Salyers, M. P., Rollins, A. L., Monroe-DeVita, M., & Pfahler, C.
(2012). Burnout in mental health services: A review of the problem and its
remediation. Administration and Policy in Mental Health and Mental
Health Services Research, 39(2), 341-352.
https://doi.org/10.1007/s10488-011-0352-1

Well-being and Burnout in Psychologists 73
Moser, G., & Rouquette, M. L. (2002). Psychology in France: A popular
discipline with a strong tradition and a somewhat uncertain future.
European Psychologist, 7(3), 238-241. https://doi.org/10.1027/1016-
9040.7.3.238
National Association of School Psychologists. (2022) Who are school
psychologists? https://www.nasponline.org/about-school psychology/who-are-
school-psychologists
National Institute for Health and Care Excellence. (2012) The guidelines
manual. Reviewing the evidence. https://www.nice.org.uk/process/pmg6
/chapter/reviewing-the-evidence
Nel, P. W., Pezzolesi, C., & Stott, D. J. (2012). How did we learn best? A
retrospective survey of clinical psychology training in the United
Kingdom. Journal of Clinical Psychology, 68(9), 1058-1073.
https://doi.org/10.1002/jclp.21882
Nicholson, E., Murphy, T., Larkin, P., Normand, C., & Guerin, S. (2016).
Protocol for a thematic synthesis to identify key themes and messages from
a palliative care research network. BMC Research Notes, 9(1), 1-5.
Norton, P. J., Norberg, M. M., Naragon-Gainey, K., & Deacon, B. J. (2022). An
examination of accreditation standards between Australian and
US/Canadian doctoral programs in clinical psychology. Clinical
Psychologist, 26(2), 181-187.
https://doi.org/10.1080/13284207.2021.1949944

Well-being and Burnout in Psychologists 74
Obama, B. (2016). United States health care reform: progress to date and next
steps. Jama, 316(5), 525-532.
O’Connor, K., Neff, D. M., & Pitman, S. (2018). Burnout in mental health
professionals: A systematic review and meta-analysis of prevalence and
determinants. European Psychiatry, 53, 74-99.
https://doi.org/10.1016/j.eurpsy.2018.06.003
Ofonedu, M. E., Belcher, H. M., Budhathoki, C., & Gross, D. A. (2017).
Understanding barriers to initial treatment engagement among underserved
families seeking mental health services. Journal of Child and Family
Studies, 26(3), 863-876. https://doi.org/10.1007/s10826-016
0603-6
Olver, M. E., Preston, D. L., Camilleri, J. A., Helmus, L., & Starzomski, A.
(2011). A survey of clinical psychology training in Canadian federal
corrections: Implications for psychologist recruitment and retention.
Canadian Psychology, 52(4), 310-320. https://doi.org/10.1037/a0024586
Pace, R., Pluye, P., Bartlett, G., Macaulay, A. C., Salsberg, J., Jagosh, J., et al.
(2012). Testing the reliability and efficiency of the pilot Mixed Methods
Appraisal Tool (MMAT) for systematic mixed studies review. International
Journal of Nursing Studies, 49(1), 47-53.
https://doi.org/10.1016/j.ijnurstu.2011.07.002
Page, M. J., McKenzie, J. E., Bossuyt, P. M., Boutron, I., Hoffmann, T. C.,
Mulrow, C. D., & Moher, D. (2021). The PRISMA 2020 statement: an
updated guideline for reporting systematic reviews. Systematic Reviews,

Well-being and Burnout in Psychologists 75
10(1), 1-11. https://doi.org/10.1016/j.ijsu.2021.105906
Pakenham, K. I., & Stafford‐Brown, J. (2012). Stress in clinical psychology
trainees: Current research status and future directions. Australian
Psychologist, 47(3), 147-155. https://doi.org/10.1111/j.1742
9544.2012.00070.x
Papanicolas, I., Woskie, L. R., & Jha, A. K. (2018). Health care spending in the
United States and other high-income countries. Jama, 319(10), 1024
1039.
Patel, R. S., Bachu, R., Adikey, A., Malik, M., & Shah, M. (2018). Factors
related to physician burnout and its consequences: a review. Behavioral
Sciences, 8(11), 98-101. https://doi.org/10.3390/bs8110098
Pisanti, R., Lombardo, C., Lucidi, F., Violani, C., & Lazzari, D. (2013).
Psychometric properties of the Maslach Burnout Inventory for Human
Services among Italian nurses: a test of alternative models. Journal of
Advanced Nursing, 69(3), 697-707.
https://doi.org/10.1111/j.13652648.2012.06114.x
Pluye, P., Grad, R. M., Levine, A., & Nicolau, B. (2009b). Understanding
divergence of quantitative and qualitative data (or results) in mixed methods
studies. International Journal of Multiple Research Approaches,
3(1), 58-72. https://doi.org/10.5172/mra.455.3.1.58
Punton, G., Dodd, A. L., & McNeill, A. (2022). ‘You’re on the waiting list’: An
interpretive phenomenological analysis of young adults’ experiences of waiting

Well-being and Burnout in Psychologists 76
lists within mental health services in the UK. Plos One, 17(3).
https://journals.plos.org/plosone/article?id=10.1371/journal.pone.02655
2
Purssell, E., & McCrae, N. (2020). How to perform a systematic literature
review: a guide For healthcare researchers, practitioners and students.
Springer Nature.
Råbu, M., Moltu, C., Binder, P. E., & McLeod, J. (2016). How does practicing
psychotherapy affect the personal life of the therapist? A qualitative
inquiry of senior therapists’ experiences. Psychotherapy Research,
26(6), 737-749. https://doi.org/10.1080/10503307.2015.1065354
Ragavan, R.N. (2018). Experiences of Black, Asian and Minority Ethnic Clinical
Psychology Doctorate Applicants within the UK [Doctoral Dissertation,
University of Hertfordshire]. University of Hertfordshire Research Archive
https://uhra.herts.ac.uk/handle/2299/21590
Richards, C., & Barrett, J. (2020). Trans and non-binary gender healthcare for
Psychiatrists, psychologists, and other health professionals. Cambridge University
Press.
Rodriguez, S. Y. S., & Carlotto, M. S. (2017). Predictors of Burnout Syndrome in
psychologists. Estudos de Psicologia (Campinas), 34, 141-150.
https://doi.org/10.1590/1982-02752017000100014
Roncalli, S., & Byrne, M. (2016). Relationships at work, burnout and job
satisfaction: A study on Irish psychologists. Mental Health Review
Journal. 21(1), 23-36 https://doi.org/10.1108/MHRJ-01-2015-0002

Well-being and Burnout in Psychologists 77
Ruisoto, P., Ramírez, M. R., García, P. A., Paladines-Costa, B., Vaca, S. L., &
Clemente Suárez, V. J. (2021). Social support mediates the effect of burnout
on health in health care professionals. Frontiers in Psychology,
11. https://doi.org/10.3389/fpsyg.2020.623587
Rupert, P. A., & Dorociak, K. E. (2019). Self-care, stress, and well-being among
Practicing psychologists. Professional Psychology: Research and
Practice, 50(5), 343-350. https://doi.org/10.1037/pro0000251 Rupert,
P. A., & Kent, J. S. (2007). Gender and work setting differences in career-
sustaining behaviors and burnout among professional psychologists.
Professional Psychology: Research and Practice, 38(1),
88 - 96. https://doi.org/10.1037/0735-7028.38.1.88
Rupert, P. A., & Morgan, D. J. (2005). Work setting and burnout among
professional psychologists. Professional Psychology: Research and
Practice, 36(5), 544-550. https://doi.org/10.1037/0735-7028.36.5.544
Rupert, P. A., Stevanovic, P., & Hunley, H. A. (2009). Work-family conflict and
burnout among practicing psychologists. Professional Psychology:
Research and Practice, 40(1), 54-61 https://doi.org/10.1037/a0012538
Ryan, C., Hesselgreaves, H., Wu, O., Paul, J., Dixon-Hughes, J., & Moss, J. G.
(2018). Protocol for a systematic review and thematic synthesis of patient
experiences of central venous access devices in anti-cancer treatment.
Systematic Reviews, 7(1), 1-7. https://doi.org/10.1186/s13643-018-
0721x

Well-being and Burnout in Psychologists 78
Sadusky, A., & Spinks, J. (2022). Psychologists’ engagement in reflective
practice and experiences of burnout: a correlational analysis. Reflective
Practice, 23(5), 593-606 https://doi.org/10.1080/14623943.2022.2090326
Sheather, J. and Slattery, D. (2021), The great resignation – how do we
support and retain staff already stretched to their limit? BMJ, 375(2533).
https://www.bmj.com/content/bmj/375/bmj.n2533.full.pdf
Sim, W., Zanardelli, G., Loughran, M. J., Mannarino, M. B., & Hill, C. E. (2016).
Thriving, burnout, and coping strategies of early and later career counseling
center psychologists in the United States. Counselling
Psychology Quarterly, 29(4), 382-404.
https://doi.org/10.1080/09515070.2015.1121135
Simpson, S., Simionato, G., Smout, M., van Vreeswijk, M. F., Hayes, C.,
Sougleris, C., & Reid, C. (2019). Burnout amongst clinical and counselling
psychologist: The role of early maladaptive schemas and coping modes as
vulnerability factors. Clinical Psychology &
Psychotherapy, 26(1), 35-46. https://doi.org/10.1002/cpp.2328
Skorupa, J., & Agresti, A. A. (1993). Ethical beliefs about burnout and continued
professional practice. Professional Psychology: Research and
Practice, 24(3), 281-288. https://doi.org/10.1037/0735-7028.24.3.281
Smith, R. (2006). Peer review: a flawed process at the heart of science and
journals. Journal of the Royal Society of Medicine, 99(4), 178-182.
https://doi.org/10.1177/014107680609900414

Well-being and Burnout in Psychologists 79
Smout, M. F., Simpson, S. G., Stacey, F., & Reid, C. (2022). The influence of
maladaptive coping modes, resilience, and job demands on emotional exhaustion
in psychologists. Clinical Psychology & Psychotherapy, 29(1),
260-273. https://doi.org/10.1002/cpp.2631
Sodeke-Gregson, E. A., Holttum, S., & Billings, J. (2013). Compassion
satisfaction, burnout, and secondary traumatic stress in UK therapists who
work with adult trauma clients. European Journal of
Psychotraumatology, 4(1). https://doi.org/10.3402/ejpt.v4i0.21869
Squires, A., Finlayson, C., Gerchow, L., Cimiotti, J. P., Matthews, A.,
Schwendimann, R., Griffiths, P., Busse, R., Heinen, M., Brzostek, T., Moreno-
Casbas, M.T., Aiken, L.H., & Sermeus, W. (2014).
Methodological considerations when translating “burnout”. Burnout
Research, 1(2), 59-68. https://doi.org/10.1016/j.burn.2014.07.001
Stern, C., Lizarondo, L., Carrier, J., Godfrey, C., Rieger, K., Salmond, S.,
Apostolo, J., Kilpatrick, P., & Loveday, H. (2020). Methodological guidance for
the conduct of mixed methods systematic reviews. JBI
Evidence Synthesis, 18(10), 2108-2118.
https://doi 10.11124/JBISRIR-D 19-00169
Stubbs, J. M., & Achat, H. M. (2022). Are healthcare workers particularly
vulnerable to loneliness? The role of social relationships and mental well being
during the COVID-19 pandemic. Psychiatry Research
Communications, 2(2), 1-12.
https://doi.org/10.1016/j.psycom.2022.100050
Summers, E. M., Morris, R. C., Bhutani, G. E., Rao, A. S., & Clarke, J. C.

Well-being and Burnout in Psychologists 80
(2021). A survey of psychological practitioner workplace well‐being.
Clinical Psychology & Psychotherapy, 28(2), 438-451.
https://doi.org/10.1002/cpp.2509
Tay, S., Alcock, K., & Scior, K. (2018). Mental health problems among clinical
psychologists: Stigma and its impact on disclosure and help‐seeking.
Journal of Clinical Psychology, 74(9), 1545-1555.
https://doi.org/10.1002/jclp.22614
Thomas, J., & Harden, A. (2008). Methods for the thematic synthesis of
qualitative research in systematic reviews. BMC Medical
Research Methodology, 8(1), 1-10. https://doi.org/10.1186/1471-2288-8
45
Toh, S. G., Ang, E., & Devi, M. K. (2012). Systematic review on the relationship
between the nursing shortage and job satisfaction, stress and burnout levels
among nurses in oncology/ haematology settings. International
Journal of Evidence‐Based Healthcare, 10(2), 126-141.
https://doi.org/10.1111/j.1744-1609.2012.00271.x
Tong, A., Flemming, K., McInnes, E., Oliver, S., & Craig, J. (2012). Enhancing
transparency in reporting the synthesis of qualitative research: ENTREQ.
BMC Medical Research Methodology, 12(1), 1-8.
https://doi.org/10.1186/1471-2288-12-181
Turnbull, M. G., & Rhodes, P. (2021). Burnout and growth: Narratives of
Australian Psychologists. Qualitative Psychology, 8(1), 51-61
https://doi.org/10.1037/qup0000146

Well-being and Burnout in Psychologists 81
Vincent, L., Brindley, P. G., Highfield, J., Innes, R., Greig, P., &
Suntharalingam,G. (2019). Burnout Syndrome in UK Intensive Care Unit
staff: Data from all three Burnout Syndrome domains and across professional
groups, genders and ages. Journal of the Intensive Care
Society, 20(4), 363-369. doi: 10.1177/1751143719860391
Vredenburgh, L. D., Carlozzi, A. F., & Stein, L. B. (1999). Burnout in
Counselling psychologists: Type of practice setting and pertinent
demographics.Counselling Psychology Quarterly, 12(3), 293-302.
https://doi.org/10.1080/09515079908254099
Walker, L. (2017). Compassion, Burnout and Self-Care in NHS Staff Delivering
Psychological Interventions [Doctoral dissertation, University of East
London]. University of East London Repository.
https://repository.uel.ac.uk/item/84qz3
West, C. P., Dyrbye, L. N., & Shanafelt, T. D. (2018). Physician burnout:
contributors, consequences and solutions. Journal of Internal Medicine,
283(6), 516-529. https://doi.org/10.1111/joim.12752
Westman, M., & Bakker, A. B. (2008). Crossover of burnout among healthcare
Professionals. In: J.R.B., Halbesleben (Eds.), Handbook of Stress and
Burnout in Health Care (pp. 111-125). Nova Science Publishers.
https://www.isonderhouden.nl/doc/pdf/arnoldbakker/articles
/articles_arnold_bakker_170.pdf
Williamson, K., Lank, P. M., Cheema, N., Hartman, N., Lovell, E. O., &
Emergency Medicine Education Research Alliance (EMERA). (2018).

Well-being and Burnout in Psychologists 82
Comparing the Maslach burnout inventory to other well-being
instruments in emergency medicine residents. Journal of Graduate
Medical Education, 10(5), 532-536. https://doi.org/10.4300/JGME-D-18-
00155.1
Wise, E. H., & Barnett, J. E. (2016). Self-care for psychologists. In J. C.
Norcross, G. R. VandenBos, D. K. Freedheim, & L. F. Campbell
(Eds.), APA handbook of clinical psychology: Education an profession (pp.
209–222). American Psychological Association.
https://doi.org/10.1037/14774-014
Zinsstag, J., Schelling, E., Waltner-Toews, D., & Tanner, M. (2011). From “one
medicine” to “one health” and systemic approaches to health and welbeing.
Preventive Veterinary Medicine, 101(3-4), 148-156.
https://doi.org/10.1016/j.prevetmed.2010.07.003
Zippia. (2023), (February 2). Psychologist demographics and statistics in the
US. https://www.zippia.com/psychologist-jobs/demographics
Well-being and Burnout in Psychologists 83
Appendices
Appendix A: PRISMA Checklist With Locations
(Adapted from Page et al., 2021)
Section and
Topic
Item
#
Checklist item
Location where the item is reported
TITLE
Title
1
Identify the report as a literature review.
Title Sheet
ABSTRACT
Abstract
2
Provide a structured summary including, as applicable: background; objectives; data sources; study eligibility
criteria, participants, and interventions; study appraisal and synthesis methods; results; limitations; conclusions and
implications of key findings.
See the PRISMA 2020 for Abstracts checklist for the complete list.
Abstract Section
INTRODUCTION
Rationale
3
Describe the rationale for the review in the context of existing knowledge, i.e., what is already known about your
topic.
Provided in the background literature
review
Objectives
4
Provide an explicit statement of the objective(s) or question(s) the review addresses with reference to participants,
interventions, comparisons, outcomes, and study design (PICOS).
Provided in the reeview aims and
objectives and methods.
METHODS
Eligibility criteria
5
Specify the inclusion and exclusion criteria for the review and how studies were grouped for the syntheses with
study characteristics (e.g., PICOS, length of follow-up) and report characteristics (e.g., years considered, language,
publication status) used as criteria for eligibility, giving rationale.
Provided in the method sections
Information
sources
6
Specify all databases, registers, websites, organisations, reference lists and other sources searched or consulted
to identify studies. Specify the date when each source was last searched or consulted.
Methods sections and appendices
Search strategy
7
Present the full search strategies for all databases, registers and websites, including any filters and limits used.
Methods and Appendices
Well-being and Burnout in Psychologists 84
Selection process
8
State the process for selecting studies (i.e., screening, eligibility).
Specify the methods used to decide whether a study met the inclusion criteria of the review, including how many
reviewers screened each record and each report retrieved, whether they worked independently, and if applicable,
details of automation tools used in the process.
Covered in the methods section
Section and
Topic
Item
#
Checklist item
Location where the item is reported
Study risk of bias
assessment
11
Specify the methods used to assess risk of bias in the included studies, including details of the tool(s) used, how
many reviewers assessed each study and whether they worked independently, and if applicable, details of
automation tools used in the process.
Covered in methods and findings
RESULTS
Study selection
16a
Describe the results of the search and selection process, from the number of records identified in the search to the
number of studies included in the review, ideally using a flow diagram.
Methods
16b
Cite studies that might appear to meet the inclusion criteria, but which were excluded, and explain why they were
excluded.
Methods and Prisma flow chart
Study
characteristics
17
Cite each included study and present its characteristics (e.g., study size, PICOS, follow-up period).
Summaries in key information table
Risk of bias in
studies
18
Present assessments of risk of bias for each included study.
Presented in the table and in the quality
assessment summary paragraph
Results of
individual studies
19
For all outcomes, present, for each study: (a) summary statistics for each group (where appropriate) and (b) an
effect estimate and its precision (e.g. confidence/credible interval), ideally using structured tables or plots. Clearly
represent which studies have identified which findings, and offer transparency around the use of outcomes
measures, country of origin, and training background of participants
Covered in methods and discussion
DISCUSSION
Discussion
23a
Provide a general interpretation of the results in the context of other evidence.
Discussion
23b
Discuss any limitations of the evidence included in the review.
Limitations and future research
23c
Discuss any limitations of the review processes used.
Limitations and future research
23d
Discuss implications of the results for practice, policy, and future research.
Limitations and future research
OTHER INFORMATION
Well-being and Burnout in Psychologists 85
Registration and
protocol
24a
Provide registration information for the review, including register name and registration number, or state that the
review was not registered.
Review not registered, not a
requirement at time of understaking the
review
24b
Indicate where the review protocol can be accessed, or state that a protocol was not prepared.
Review not registered, not a
requirement at time of understaking the
review
24c
Describe and explain any amendments to information provided at registration or in the protocol.
Review not registered, not a
requirement at time of understaking the
review
Section and
Topic
Item
#
Checklist item
Location where the item is reported
Support
25
Describe sources of financial or non-financial support for the review, and the role of the funders or sponsors in the
review.
N/A for Dclin
Competing
interests
26
Declare any competing interests of review authors.
N/A for Dclin
Availability of
data, code, and
other materials
27
Report which of the following are publicly available and where they can be found: template data collection forms;
data extracted from included studies; data used for all analyses; analytic code; any other materials used in the
review.
Full titles and authors of papers are
provided
Well-being and Burnout in Psychologists
91
Appendix B: Full Search Terms
Database
Search
Terms
MEDLINE
PsychInfo
Webb of Science
1 ("burnout" and
"psychologist*" and (stress* or
"emotional exhaustion*" or
pressure or coping or manage* or
"well-being" or "mental health" or
"work related stress" or
"compassion Fatigue"))
1 ("burnout" and
"psychologist*" and
(stress* or "emotional
exhaustion*" or pressure
or coping or manage* or
"well-being" or "mental
health" or "work related
stress" or "compassion
Fatigue")).
1 "burnout"
2 Limit 1 to'll adult (19 plus
years)
2 limit 1 to
"300 adulthood <age 18
yrs and older>"
2 Psycholigist*
3 Burnout, Psychological/*
3 exp Occupational
Stress/*
3 (stress* OR "emotional
exhaustion*" OR
pressure OR coping OR
manage* OR "wellbeing"
OR "mental health" OR
"work related stress" OR
"compassion
Fatigue")
Well-being and Burnout in Psychologists
92
4 Occupational Stress/*
4 exp Psychologists/*
4 1, 2 and 3
5 3 and 4
5 3 and 4
6 1 or 5
6 1 or 5
7 Limit 6 to "all adult (19 plus
years)"
7 Limit 6 to
"300 adulthood <age 18
yrs and older>"
Results
/* Database specific MeSH terms

Well-being and Burnout in Psychologists 93
Appendix C: Sample of the Extraction Table
Part 1
Well-being and Burnout in Psychologists 94


Well-being and Burnout in Psychologists
95
Appendix D: JBI Checklist for ACS
Item
Question
1
Were the criteria for inclusion in the sample clearly defined?
2
Were the study subjects and the setting described in detail?
3
Was the exposure measured in a valid and reliable way?
4
Were objective, standard criteria used for measurement of the
condition?
5
Were confounding factors identified?
6
Were strategies to deal with confounding factors stated?
7
Were the outcomes measured in a valid and reliable way?
8
Was appropriate statistical analysis used?
Comments:
Response Options: Yes, No, Unclear or Not Applicable

Well-being and Burnout in Psychologists
96
Appendix E: JBI Checklist for Qualitative Research
Item
Question
1
Is there congruity between the stated philosophical perspective and the
research methodology?
2
Is there congruity between the research methodology and the research
question or objectives?
3
Is there congruity between the research methodology and the methods
used to collect data?
4
Is there congruity between the research methodology and the
representation and analysis of data?
5
Is there congruity between the research methodology and the
interpretation of results?
6
Is there a statement locating the researcher culturally or theoretically?
7
Is the influence of the researcher on the research, and vice- versa,
addressed?
8
Are participants, and their voices, adequately represented?
9
Is the research ethical according to current criteria or, for recent
studies, and is there evidence of ethical approval by an appropriate
body?
10
Do the conclusions drawn in the research report flow from the analysis,
or interpretation, of the data?
Comments:

Response Options: Yes, No, Unclear or Not Applicable

Well-being and Burnout in Psychologists 97
Appendix F: Summary of Thematic Synthesis Theme Development for Quantitative Data
Analytical
Theme
Descriptive Theme
Example Codes
Example Quotes
Presence of
Burnout
Burnout Outcome
Measures
Lower than standard norms, higher than standard
norms, sever/ high burnout, mild burnout,
moderate burnout, high emotional exhaustion,
high depersonalisation, low personal
accomplishment.
‘Mean emotional exhaustion (EE), depersonalisation (DP) and
personal accomplishment (PA) were significantly higher than
MBI standards for mental health workers’, ‘49.2% of
participants scored in the high burnout range’
Demographic
Characteristics
Age and Gender
Women, men, older psychologists, younger
psychologists, age.
‘Younger psychologists scored higher on EE than older peers’,
‘…correlations indicated that younger age was related to higher
burnout.’, ‘Females had significantly higher personal burnout.’
Occupational
Experiences
Work Setting, Years’
Experience and the
Impact of the Work
Early career psychologists, newly qualified
psychologists, private practice, agency
psychologists, job satisfaction, caseload,
relationships with colleges, job demands,
roleconflict.
‘Role conflict was positively correlated with disengagement.’,
‘Psychologists in private practice experienced less emotional
exhaustion, less depersonalisation, and more personal
accomplishment’
Personal
Resources
Humour, Beliefs about
Burnout and Coping
Self-defeating humour, self-enhancing humour,
positives associated with humour, believe burnout
‘Unrelenting Standards Early Maladaptive Schemas were most
highly endorsed by both the low and high burnout group’,

Well-being and Burnout in Psychologists 98
is unethical, maladaptive coping modes, early
maladaptive schema, self-sacrificing
‘Self-defeating humour (β = .32, p < .001) had the biggest
negative impact on psychologist’s burnout’
Social Support
Networks
Talking to Family and
Friends
Less social support, work-family conflict, talking to
friends, discussing frustration with family.
‘Discussing work frustrations with family, friends or colleagues
positively correlated with overall burnout’, ‘greater burnout
was associated with less social support’


98
Well-being and Burnout in Psychologists
SCHOOL OF PSYCHOLOGY
DOCTORATE IN CLINICAL PSYCHOLOGY
Empirical Research Project
Well-being and Clinical Psychology Training: An exploration of clinical
psychologist’s learning experiences through clinical training and the
impact post-qualification.
Trainee Name: Amy Claire Peters
Primary Research Supervisor: Dr Cordet Smart
Secondary Research Supervisor: Dr Rachel Handley
Target Journal: British Journal of Clinical Psychology
Word Count: 11,773 (excluding abstract)
Submitted in partial fulfilment of requirements for the Doctorate Degree in Clinical
Psychology, University of Exeter

Well-being and Burnout in Psychologists 99
Abstract
Background: Clinical psychologists (CPs) can experience poor wellbeing
due to their professional demands (Bettney., 2017). Clinical psychology training
programmes must support CPs in developing their ability to manage their well-
being (Myers et al., 2012 BPS., 2017); however, to the researcher’s knowledge,
no research explores CPs' experiences of learning about well-being through
training. Thus, the current study aims to address this gap and explore the impact
of this learning post-qualification.
Methods: Twelve recently qualified clinical psychologists participated in
semistructured interviews exploring their well-being-related learning experiences
during training. Transcripts were analysed using interpretive phenomenological
analysis (IPA) to generate key themes.
Findings and Discussion: Four key themes were identified across participants’
experiences. These were: implicit messages about well-being, wellbeing is not
prioritised, connection maintains well-being and inadequate preparation for
post-qualification challenges. Findings highlight the importance of organisational
culture and implicit communication in CPs' learning experiences.
Clinical Implications: Course providers should carefully attend to what and how
messages about well-being are communicated to trainee CPs during training to
maximise opportunities to prepare CPs to take a sustainable approach to their
well-being.
Keywords: Well-being, Clinical Psychology, Clinical Psychologists, Training,
Meaning Making

Well-being and Burnout in Psychologists 100
Introduction
Clinical psychologists (CPs) are susceptible to poor well-being due to
workrelated stressors, including large caseloads, insufficient staffing, and the
emotional impact of working with clients experiencing emotional distress (Myers
et al., 2012; Bettney., 2017). CP’s well-being warrants investigation for several
reasons. Firstly, it can have profound psychological consequences, including
burnout, depression, and anxiety (Jones & Thompson., 2017; McCormack.,
2018; Richardson et al., 2020). There may also be adverse consequences for
patient safety, with poor well-being linked to increased clinical errors (Hall et al.,
2016). Lastly, many CPs are leaving the NHS workforce and stating workrelated
stressors, unsustainable working conditions and poor work-life balance as
reasons for leaving (Ahmed et al., 2022; Shemtob et al., 2022). With a 14%
vacancy rate for NHS CP posts (HEE., 2021; Deakin, 2022), well-being presents
a significant concern in ensuring the NHS is sufficiently staffed to meet the ever-
increasing demand for services (Baker., 2020; HEE., 2021).
Given the significant impact of staff well-being and the emotional impacts
of COVID-19 on healthcare workers, it is unsurprising that the NHS has faced
increased pressure to support the well-being of their workforce (The Kings Fund.,
2018; Clarkson et al., 2023). Individual clinicians are also being encouraged to
proactively manage their well-being (Bettney., 2017; Walker., 2017). Historically,
research on CP well-being focused on identifying workrelated stressors and
developing interventions to improve well-being (Cushway, 1992; Hannigan et al.,
2004; Pakenham & Stafford‐Brown., 2012; Pakenham., 2015). CPs complete a
rigorous doctoral training programme that presents opportunities for varied and

Well-being and Burnout in Psychologists 101
immersive learning in various areas, including personal and professional
development, such as well-being (British
Psychological Society, BPS., 2017). Currently, no research explores CP's
wellbeing-related learning during this period. Thus, the current addresses this
gap by exploring CP’s experiences of learning about well-being during training
and the impact of this learning post-qualification.
Defining Well-being
Staff well-being has become a key consideration in occupational health
due to the recognition of its relationship to workplace productivity and staff
retention (Simons & Baldwin., 2021). There is a lack of consensus on the
definition of well-being (Forgeard et al., 2011; Dodge et al., 2012; Simons &
Baldwin., 2012); however, it is generally accepted that it is a state in which an
individual experiences positive feelings, growth, and a sense that they can meet
their potential in a given environment (Simons & Baldwin., 2021). It
encompasses biological, social, and psychological factors such as demands
and resources (Dodge et al., 2012) and can fluctuate over time. An integral
concept of well-being is a desire to achieve equilibrium or stasis (Cummins.,
2010).
A historical review of occupational well-being models is provided by
Schmidt and colleagues (2019); however, the Job-Demands Resource Model (J-
DRM) is often cited as a helpful way to operationalise workplace well-being in
healthcare settings(Bauer et al., 2014). The J-DRM suggests that occupational
experiences can be divided into two categories. The first, Job demands, refers to
the aspects of one's role that require sustained effort (such as high workloads)

Well-being and Burnout in Psychologists 102
and are associated with biological, psychological and social costs (Bakker and
Demerouti, 2017). Personal resources are the second category, which refers to
aspects of the job that help to support one's ability to reach work-related goals
and improve their occupational experience. Job and personal resources (such
as relationships with colleagues and optimism) work to reduce the costs
associated with job demands and stimulate personal growth (Demerouti et al.,
2001; Xanthopoulou et al., 2009). Although the J-DRM receives criticism for lack
of distinction between processes, such as what constitutes a demand or
resource or the role of internal motivation (Taris & Schaufeli., 2018), the model
provides a robust conceptualisation of well-being for occupational research
(Schaufeli, 2017).
Well-being in Clinical Psychologists
Historically, psychologists neglect the importance of developing and
maintaining a balance between caring for others and the self (Wise et al., 2012).
This is reflected in research indicating that CPs are at high risk of experiencing
work-related distress and burnout (Lee et al., 2011; Bettney., 2017). During training,
competing clinical, research, and academic demands, alongside the anxiety caused
by constant evaluation, have been consistently shown to impact trainee CP’s well-
being negatively (Cushway., 1992; Hannigan et al., 2004; Pakenham & Stafford-
Brown, 2012; Pakneham., 2015).
Trainee CPs must inevitably transition from students to qualified
practitioners, which can be a challenging period for the well-being of healthcare
professionals, including CPs (Van Den Broek et al., 2020; Levinson et al., 2021).
According to Melesis Transition Theory (Meleis et al., 2010), healthcare workers

Well-being and Burnout in Psychologists 103
may experience disconnection from previous social or organisational support
structures, loss of reference points, new responsibilities, and increased
autonomy when transitioning to qualified practice. Understanding the potentially
stressful experience of transitioning from a trainee to a qualified CP is important
in understanding how the well-being of CPs may change over time and
identifying periods that may pose a more significant threat to CP's well-being. It
may also help to identify opportunities for meaningful intervention, which may be
beneficial targets for explorative research (Levinson et al., 2021). Once
qualified, CPs continue to experience stressors now relating to job demands,
large caseloads, and working in isolation (Myers et al., 2012; Bettney., 2017).
Supporting clients experiencing emotional distress can lead to the experience of
vicarious trauma, the negative effects of which are well documented (Lim et al.,
2010; Makadia et al., 2017). Research has highlighted that many psychologists
are experiencing burnout and report significant challenges in maintaining work-
life balance (McCormack et al., 2018). Maintaining well-being and engaging in
self-care can help to reduce the risk of burnout in CPs (Rupert & Dorocaik.,
2019). The current provision of well-being learning opportunities on DClinPsy
courses may unwittingly contribute to a professional culture in which
psychologists struggle to connect with a need to prioritise their well-being (Wise
et al., 2012). With recently qualified CPs at continued risk of poor well-being, we
must fully understand the role of this highly formative clinical training period
(BPS., 2019) in preparing CPs to manage their well-being throughout their
careers. Maintaining well-being and engaging in selfcare can help to reduce the
risk of burnout in CPs (Rupert & Dorocaik., 2019). The current provision of well-

Well-being and Burnout in Psychologists 104
being learning opportunities on DClinPsy courses may unwittingly contribute to a
professional culture in which psychologists struggle to connect with a need to
prioritise their well-being (Wise et al., 2012).
Upon completing the doctorate, many CPs continue to work in the NHS
(Odusanya et al., 2018). Most recent figures published in 2019 showed that
20,000 psychological professionals worked within the NHS, with CPs accounting
for over 42% of the psychological profession's workforce (HEE., 2021). The
demand for psychologists is increasing, with plans to train and recruit 2,520
additional psychologists into the workforce by 2024 (HEE., 2021). Though poor
well-being has become an increasing concern for CPs throughout their careers,
those at an early career stage or in training may be particularly susceptible
(Pakenham & Stafford‐Brown, 2012; Rose et al., 2019). To support the
expansion of the CP workforce, it is fundamentally important that we understand
more about CPs' experience of learning about well-being in the early stages of
their careers, including training and the transition into postqualification.
Clinical Psychology Training, Learning, and Well-being
To become a CP in the UK, individuals complete a three-year Doctorate in
Clinical Psychology Programme (DClinPsy) in one of the 30 approved training
institutions. The training follows a competency-based training model to support
the development of doctoral standard academic, clinical and research skills
(Kenkel & Peterson., 2010). Trainees are also required to meet an appropriate
level of personal and professional development (Nel et al., 2012).
The DClinPsy is a post-graduate adult learning experience which utilises
formal and informal experiential work-based learning (Costley & Lester., 2012; Nisbet

Well-being and Burnout in Psychologists 105
et al., 2013). Learning occurs through attendance at clinical placements, formal
learning (e.g., university lectures and workshops) (Choi and Jacobs,
2011), and independent learning through completing a research thesis (Nel et al., 2012). In
preparing CPs for NHS careers, training programmes must provide structured opportunities for
strategy development for well-being (Gockel., 2010; Pakenham & Stafford-Brown, 2012). Of the
nine core competencies and 71 sub-competencies for CPs in training, only two sub-
competencies recognise the importance of trainee well-being. The BPS does not provide
specific directions on how to support trainee CPs to meet these well-being-related
competencies (BPS., 2017). As such, CP's learning experiences will likely vary significantly
across DClinPsy courses. Literature searches did not reveal any research exploring what CPs
learn about well-being during training (BPS., 2017); however, research does suggest that
training programmes do not adequately support trainee CPs to develop strategies for well-being
maintenance (Lambert & Simon, 2008; Myers et al., 2012; Brettney., 2017). Despite there being
a role for DClinPsy courses in supporting CPs to learn about well-being, the paucity of research
exploring the learning experiences of CPs presents a significant gap in the research
understanding of the impact of training on CP's well-being throughout their careers.
Individuals' learning experiences are shaped by their pre-conceived
assumptions, knowledge and experiences, which are heavily influenced by their
experience of the world. Through learning, individuals attempt to understand and
give meaning to their experiences (Billett, 2008; Nevalainen et al., 2018). During
the DClinPsy, each trainee CP experiences individualised learning; however, for
NHS staff, Organisational culture (OC) can enhance or inhibit their learning
experience (Davies & Nutley., 2000). OC refers to ways of thinking, feeling, and
behaving shared by individuals in a healthcare organisation

Well-being and Burnout in Psychologists 106
(Mannion & Davies., 2018). Culture is a fundamental part of the stories and narratives
organisations, teams, and subsequently, individuals learn to hold about why things are done in a
certain way (Simpson et al., 2019). It provides individuals with guidance on how they are
expected to think, feel and behave in relation to a range of topics, such as well-being
(Nanayakkara & Wilkinson., 2022).
According to Schein (1990), there are three levels of OC, which help to
demonstrate the potential impact of OC on CP's experiences of learning about
well-being. Artefacts are the shallowest indicator of OC; they refer to the visible
indicators of culture, such as dress codes, banding or role titles, and office
layouts (Davies 2002; Mannion & Davies., 2018). Organisational values, mission
statements, and written communications are all examples of espoused values.
These are deeper aspects of OC that would create some noticeable change to
overall OC in an organisation such as the NHS (Scott et al., 2003).
The deepest and arguably most important aspect of OC, according to Schein
(1990), comes from underlying beliefs and assumptions; these reflect
individually held assumptions about how employees should perform, interact
with others, and conduct themselves. These are the strongest indicator of what
an organisation is like; they are often held by the individual, hard to access, and
even more challenging to influence (Al Saifi., 2015). These aspects of OC can
significantly impact the overall content and process of the learning experience
for healthcare workers (Davis & Nutley., 2000).
During their training, CPs are uniquely positioned as they experience their
learning within the context of two large organisations, the NHS and their host
university. The NHS culture for frontline staff has long been characterised by the

Well-being and Burnout in Psychologists 107
expectation to start work early, finish late, and to subjugate one's needs for the
needs of the patients (Mackenzie., 1995). In addition, emotional stoicism, or the
tendency to endure hardship without complaint, or external expression of the
distress caused, is highly valued in the NHS culture (McCarthy et al., 2020). The
OC relating to senior management in UK universities has received some
research attention (O’Connor., 2011); however, the review of the evidence
provided little research exploring the student experience of OC at UK
universities. There are several reported similarities in the culture across the NHS
and Universities in the UK; for example, due to an increase in the use of national
frameworks, focus on auditing, and producing outcome and performance data,
both incorporate aspects of a hierarchical culture (Jacobs et al., 2013). As OC is
such a nuanced element of organisational life, there are likely differences or
conflicts in the underlying beliefs and assumptions held by individuals across
these organisations (Sagiv & Schwartz., 2007), which CPs will experience in
their well-being learning journey. Adapting to and integrating the experience of
university and NHS cultures is not dissimilar to the notion of acculturation
(Thacker et al., 2022). Acculturation refers to the process in which people adapt
to the dominant culture in a specific environment while retaining some of their
cultural values and beliefs. Though this is often used in relation to the
experiences of people from multicultural backgrounds, it is helpful to consider
this process concerning the learning experiences of CPs during clinical training.
OC is both an individual and group phenomenon. The individual aspect of
OC, which is concerned with the sense-making of the individual in relation to
aspects of culture, such as the impact of underlying assumptions and beliefs, is

Well-being and Burnout in Psychologists 108
often overlooked but is, in fact, imperative in the manifestation and maintenance
of OC (Harris., 1994; Dougherty & Smythe., 2004). Based on this, it is
reasonable to suggest that an exploration of CP's learning experiences relating
to well-being, and the OC context in which they take place, could be beneficial
in further understanding CPs' learning and ongoing maintenance of their
wellbeing. Moreover, understanding the culture around well-being is essential in
creating change to unhelpful aspects of OC (Scott et al., 2003).
Interpretive Phenomenological Analysis
Well-being is arguably an individual learning experience which occurs in
a wider cultural context. For CPs, the underlying beliefs and behaviours they are
exposed to in their OC and subcultures will likely influence their sensemaking
experiences in the learning process (Mahler., 1997). In their review of best
practices for DClinPsy learning, Nel and colleagues (2012) argue that a
qualitative approach to research utilising semi-structured interviews is required
to obtain a more in-depth understanding of CPs' lived experiences of learning
during clinical training.
IPA is a qualitative analysis method that, by focusing on an individual’s
sense–making, provides an ideographic approach to exploring specific events or
experiences (Alase., 2017). IPA allows researchers to present interpretive
findings which may be transferable to an appropriately homogenous group of
CPs in the UK (Smith et al., 2022). Therefore, IPA is an appropriate method of
analysis for the proposed research as it allows the researcher to draw out the
ideographic learning experience related to well-being, including consideration of

Well-being and Burnout in Psychologists 109
underlying beliefs and assumptions. Simultaneously, it allows for consideration
of the broader cultural impact on CPs sense-making experiences (Smith et al.,
2022).
The Rationale for the Current Research
This brief review of the literature illustrates that CPs are highly trained
and highly-skilled assets which are critical in the composition of the
psychological professions workforce and delivery of NHS services. Despite a
vast body of research detailing CP's experiences of poor well-being, and the
adverse consequences of this, there is an absence of research which explores
what and how UK-trained CPs learn about well-being through training. This
research aims to address this gap by exploring the well-being learning
experiences of CPs during training and the subsequent impact of this learning on
their post-qualification experiences.
This exploration may have several benefits. Firstly, it expands the current
research field beyond identifying work-related stressors and the subjective
wellbeing experience and into the somewhat overlooked area of well-being
learning experiences. Moreover, it shines a light on the lived experience of CPs
in learning about well-being, with a particular emphasis on what it is like to
experience this learning in the context of the beliefs and assumptions held by
organisations such as the NHS and DClinPsy host universities. The
research may enable researchers to make recommendations to course
providers to ensure that training programmes maximise the learning opportunity
to prepare CPs to manage their well-being throughout their NHS careers
sustainably. In addition, understanding the impacts on their early
postqualification experiences of well-being would be beneficial in understanding

Well-being and Burnout in Psychologists 110
how this learning is carried into their post-qualification experiences and provides
similar opportunities for recommendations to NHS trusts supporting newly
qualified CPs in their transition to qualified practice.
To achieve these aims, the researchers intend to answer the following research
questions:
1. What are clinical psychologists' experiences of learning about well-being
during training?
2. How does this learning impact clinical psychologists' experience of wellbeing
post-qualification?
Method
Methodology
The researcher is aligned with a cultural relativist stance, which dictates
that there is no one truth (Thomas & Yahix., 2016). The researchers believed
that each CPs' sense-making would be based on their societal context and could
change over time (Peat et al., 2018). An emic epistemology was selected to
underpin the research, allowing the researchers to explore CPs' experiences of
learning about well-being through the participant's perspectives, beliefs and lived
experiences.
Ethical Approval
Ethical approval was granted by the University of Exeter Psychology Ethics
Committee (Appendix A). Participation was voluntary. Participants were able to
able to withdraw up to one month after their interview. After this time, participant
data were anonymised, and the link document was destroyed.

Well-being and Burnout in Psychologists 111
Participants
Clinical Psychologists who graduated from a UK-based Doctorate in Clinical
Psychology course in the last two years (between 2018 and 2020) were invited to
participate. The BPS does not define the ‘newly qualified period for CPs, so this
time frame was chosen as it would capture newly qualified psychologists able to
recall their training and newly qualified experiences in detail required for the study.
Recruitment
Participants were recruited via Facebook and Instagram using a research
poster (Appendix B) posted in groups specifically for CPs or related to clinical
psychology (Appendix C). Participants who expressed interest via email were
sent the participant information sheet (Appendix D) and encouraged to email the
researcher with any questions.
Participants completed a consent form (Appendix E) and a demographic
questionnaire via Qualtrics (Appendix F). Demographic characteristics (age,
gender, ethnicity and sexual orientation) were collected to enable comparison with
national data. Many CPs work with their training course providers
postqualification. To ensure participants could express their experiences fully, they
were not asked to report their training course; however, during transcription,
researchers identified that each participant completed their training at a different
training programme.
The interview was arranged via email, and the participants were sent a
Zoom link to a secure virtual room. Twelve participants completed the interview;
however, one participant's data was removed from the before analysis due to
issues with the recording quality.

Well-being and Burnout in Psychologists 112
Table 1
Participant Characteristics
Participant
ID
Age
Gender
Identity
Ethnicity
Sexual
Orientation
P1
26-
34
Woman*
White – British *
Heterosexual
P2
18-
25
Woman*
White – British *
Heterosexual
P3
26-
34
Woman*
White – British *
Prefer not to say
P4
26-
34
Woman*
White – British *
Heterosexual
P5
35-
44
Woman*
White -Irish
Heterosexual
P6
26-
34
Woman*
White – British *
Bisexual
P7
26-
34
Woman*
White – British *
Heterosexual
P8
26-
34
Woman*
White – British *
Heterosexual
P9
26-
34
Woman*
White – British *
Heterosexual
P10
26-
34
Woman*
White – British *
Heterosexual
P11
35-
44
Woman*
Black / Black British/ Caribbean/
African
Heterosexual
P12
26-
34
Woman*
White – British *
Heterosexual
*Including transgender woman
* Including English/ Welsh/ N Irish and Scottish
Grey indicated the participants whose data was removed

Well-being and Burnout in Psychologists 113
Design
The study utilised individual semi-structured interviews, and Interpretive
Phenomenological Analysis (IPA) was used to analyse the data and generate themes
related to the participant's meaning-making experiences.
Semi Structured Interviews
Interview Schedule
A semi-structured interview schedule (Appendix G) was developed in four
stages:
1. Existing literature was reviewed alongside the research questions, and
questions were drafted.
2. The draft schedule was shared with the research team, a senior research
associate at an independent university, and a clinical psychologist and
academic tutor on a clinical psychology doctorate programme.
3. Edits, including the addition of prompts (e.g., ‘could you say more about how
you learned X?’) and making questions more specific to focus on the
experience of well-being (e.g., can you tell me about your well-being journey
as a CP? were made to improve the schedule.
4. A pilot interview was completed with a newly qualified CP with less than one
year of post-qualification experience. Minor amendments were made to
improve flow and generate prompts (e.g., asking participants to consider
different types of learning, such as formal, informal, etc.).

Well-being and Burnout in Psychologists 114
Procedure
Participants joined the interview using the zoom link provided. Before starting the audio
and video recording, participants were reminded of the following:
1. The research aims and given another opportunity to ask questions.
2. Their right to choose not to respond to any question without providing a reason and to
stop the interview at any time without reason.
3. The removal of identifiable data at the transcription stage.
Interviews lasted approximately 60 minutes. At the end of the interview, the
recording was stopped, and participants were given time to ask any final
questions related to the project and debrief informally with the researcher. After
the interview, participants were emailed the debrief sheet (Appendix H) and a £15
Amazon voucher.
Methods of Analysis
Consideration of Analysis Method
The researchers considered several methods of analysis consistent with
the epistemological stance. Narrative analysis would have enabled the
exploration of CP's meaning-making by exploring the language they used to
construct their stories (Herman & Vervaeck., 2019), whilst discourse analysis
would have supported an exploration through CPs language-in-use (Paltridge.,
2021). Ultimately, IPA was chosen to explore well-being through CPs
sensemaking experiences (Smith et al., 2021), which felt best suited to exploring
the emotional experience of learning about well-being (Colville et al., 2016), and
the ideographic experience of beliefs and assumptions related to OC. An

Well-being and Burnout in Psychologists 115
ideographic approach allows the researchers to explore how CPs' beliefs about
well-being are shaped by their actions and experiences and how these continue
to shape future beliefs (Murphy, 2021). IPA is well suited to analysing small
homogenous samples where participants have direct experience of the
phenomena of interest (Peat et al., 2018), and is beneficial for analysing data
with limited prior evidence in the field, as in this study (Creswell & Creswell,
2017).
IPA draws from three philosophical concepts: ideography, phenomenology
and hermeneutics. Ideography is the cornerstone of IPA and underpins the
researcher's epistemological stance. An ideographic approach to analysis
enabled the researchers to shift the focus away from attempts to generalise the
well-being experiences of CPs across the UK and instead champion the
importance of understanding the individual lived experience (Smith., 2022).
Ideography helped generate findings that may be transferable to the wider
experience of some trainees but do not claim to prove or disprove the group's
experience as a whole (Biggerstaff & Thompson., 2008).
Phenomenological principles were applied through the consideration of
the CPs' perspective on their experiences learning about well-being, particularly
their embodied experiences and how they make sense of their relationship to
learning, well-being, clinical training and post-qualification (Miller et al., 2018);
Love et al., 2020). Finally, the double hermeneutic, which refers to the impact
researcher’s attempts to make sense of the CPs own sense-making experiences
has on the interpretation of data, was particularly important to consider in this

Well-being and Burnout in Psychologists 116
research due to the researcher's status as a trainee clinical psychologist (Alase.,
2017).
In IPA, reflexivity is the process through which the researcher reflects on their beliefs
and experiences and considers their impact on the analysis process. Clarity and
transparency regarding the researcher's relationship to the data are crucial in IPA
(Nizza et al., 2021). Engaging in personal reflexivity allowed the researcher to
acknowledge their closeness to the phenomenon of interest, values and beliefs and
how these may influence all stages of the research process.
IPA Process
Smith et al.’s (2021) guidance for conducting IPA was used to support the
analysis process. The researcher used a free coding approach to immerse
themselves in the participants' experiences and allow themselves to be
presumptive, biased, creative, and unsystematic in their annotations (Larkin &
Thompson., 2012). It allowed the researcher a space to reflect on their own
biases, e.g. free coding an experience as ‘harmful’ to find that participant later
described it as helpful.
Next, initial descriptive, linguistic and interpretive coding focused on
experience and meaning-making was completed on a new copy of the transcript
(Appendix I). Descriptive coding provided a summary of the content. Linguistic
coding highlighted repetition or phrasing considered interesting to the
researcher, e.g., repetitive use of the word detrimental was coded for P5.
Interpretive coding was generated by noting the researcher's questions about the
data; for example, ‘is the participant expressing frustration here? Was coded
tentatively as ‘Frustration?’

Well-being and Burnout in Psychologists 117
These three levels of coding were summarised in experiential
statements, which captured participants' emotional experience or
meaningmaking concerning their well-being experiences. Experiential
statements (ES) were printed and pinned onto a board in random order
(Appendix J). ES with similar themes were grouped in one area of the board and
labelled as emerging themes based on their connection, e.g., competing
demands, constant assessment, and others' expectations. Personal experiential
themes (PETs) were identified by grouping related emerging themes and
naming the PET based on the shared connection across emerging themes. This
process took place several times for each transcript. Each time a picture of the
PETs and included ES was taken as a record before re-arranging the ES to
consider alternative connections and groupings.
Once each transcript had been analysed, the overarching group
experiential themes (GETs) across transcripts were identified using the same
process as PETs (example provided in Appendix K). GETs were grouped based
on their similarities; several different groupings were recorded and discussed with
the researcher supervisors and colleagues in a University of Exeter IPA working
group. The final decision on GETs grouping was based on the researcher's
reflexive interpretation of the data.
Credibility
Data collection, analysis and interpretation were routinely discussed with
supervisors and an IPA working group at Exeter University to support credibility.
The analysis process and findings were presented at an academic conference at
the University of Exeter which offered an opportunity for critical review from

Well-being and Burnout in Psychologists 118
multiple perspectives. Transparency is imperative for the credibility of IPA
research (Levitt et al., 2018). Examples of individual and group analysis are
provided for transparency.
Reflexivity
Reflexivity is integral to the rigour and credibility of qualitative research
(Smith., 2011a). To support this research, I engaged in an IPA working group
(Smith et al., 2022), reflective journaling (Vicary et al., 2017), bracketing (Alase.,
2017), and consultation (Miller et al., 2018). Provided below is an overview of
how I used these methods to enhance reflexivity and rigour, along with examples
of reflexivity in action.
IPA Working Group
I attended an Exeter University IPA working group facilitated by an
experienced IPA researcher. A log of discussions from the IPA group can be
found in Appendix L. When coding data, feedback from the group highlighted
that the initial coding was heavily interpretive and missing descriptive content. In
one instance, when discussing well-being, the participant said, ‘…actually, there
is a lot of lip service to it’ which I initially coded as ‘Well-being Is insincere or
tokenistic’. By sharing the transcript with the IPA group, I realised that I was
focusing on a higher level of interpretation than was appropriate at this stage
and that the missing descriptive coding was a necessary part of the interpretive
process. As a result, the coding was changed to ‘well-being can feel like
lipservice with ‘insincere?’ as an additional code. This experience helped ensure
that the original data was identifiable in all interpretive comments throughout the
rest of the analysis process.

Well-being and Burnout in Psychologists 119
Reflective Journal
I kept a reflective journal where I explored my values, beliefs, feelings, and
experiences concerning the research process (Vicary et al., 2017)
(Appendix M). During an early interview, when describing their well-being experience, one
participant stopped describing their experience and said, ‘Well, you know how it is’. Using the
journal to capture post-interview reflections, I became aware that the participant had assumed
my experience as a trainee CP aligned with their own, inhibiting their sense-making description.
From the next interview, I was attentive to conversational cues, which suggested the participant
had assumed I had prior knowledge. I was careful to ask participants to expand on their
experiences by adding an additional prompt to my interview schedule (‘‘I’m really interested in
your experience. Please carry on if it feels comfortable.’). Doing this allowed me to feel I was
giving participants adequate space to tell their stories and minimise assumptions about my pre-
existing knowledge or training experience.
I also reflected on the interviews immediately after they took place. I
regularly met with a fellow IPA researcher to discuss our reflective journal entries.
Following my second interview, I noted, ‘[Participant] talked about how they were
making sense of some of their experiences for the first time in the interview.
Curious about why this might be?’ Together we wondered if this was the first
opportunity the participant had to reflect on this aspect of training. As a result of
this discussion, I noticed that within my sense-making experiences, I started to
feel as though CPs were placing themselves in a vulnerable position by taking
part and discussing their experiences for the first time. I also noticed increased
pressure to ensure the research did justice to participants' experiences.

Well-being and Burnout in Psychologists 120
Consultation
I sought consultation from a CP in a local NHS trust. When developing the
research questions, they highlighted the initial question, ‘What are clinical
psychologists’ experiences of well-being during training? was too broad and may
not capture participants' well-being learning experiences. Reflexive
conversations with the CP revealed this lack of specificity was rooted in my
knowledge of the DClinPsy training process and assumptions that others might
consider learning about well-being to be part of the DClinPsy experience. This
highlighted the importance of having reflexive spaces throughout the process to
attempt to re-position myself as a researcher rather than a trainee CP. For
example, when coding the data, I would ask myself, ‘Is that your sense as a
researcher or CP?’. Though I acknowledge that from an IPA perspective, I can
not separate myself as a researcher from my lived experience, this was a useful
way to balance informing and not biasing the analysis process.
Both research supervisors worked on DClinPsy courses which created
complexity regarding credibility due to the closeness of the research team to the
phenomenon of interest. This was evident in discussions about emerging themes
where it was sometimes difficult to consider the role of responsibility for well-
being from different perspectives. My research supervisors had alliances with
course staff whilst I attempted to balance my lived experience as a trainee with
my position as a researcher. There was also an imbalance of power between the
supervisee and supervisor, making it very difficult to hold these differing views
equally worthy of consideration. To contrast the internal perspectives held by the
research team, I consulted with an IPA-focused

Well-being and Burnout in Psychologists 121
Research Associate at an external university who had no affiliation with
DClinPsy training. The consultant’s unfamiliarity with the DClinPsy process was
helpful in re-positioning the discussion to more of an outsider position. In doing so,
I identified that the power imbalance between myself and my supervisor made me
feel I needed to prioritise my supervisor's views in the analysis and interpretation.
As a result, the views of participants were getting lost. Reflexive discussions with
an external critical perspective helped prioritise participants' voices. Reflexivity is
explored further in the reflexive statement (Appendix O).
Findings
This study examined CPs experience of learning about well-being during
training and how their learning about well-being impacted their post-qualification
experiences. The overarching GETs are represented in Figure 2. GETs relating
to participants' experiences during and after training highlight differences in the
challenges to well-being faced in the trainee period compared to
postqualification. For example, participants experienced fluctuating pressures
from competing academic, clinical and research demands. In contrast, once
qualified participants experienced pressure aligned more with increased
responsibility and specific service demands. The overarching GETs encompass
participants' lived experience of well-being pre and post-qualification. Though
they are not directly related to the research question, they have been included in
Figure 2, as they highlight the qualitative differences in experience during and
after training, which helps to understand how the learning during training was
not always helpful.

Well-being and Burnout in Psychologists 122
The main learning experiences were identified in four GETs (highlighted in
yellow in Figure 1). These were selected for discussion as they most directly
address the research question relating to CPs' learning experiences related to
well-being and post-qualification impact. How CPs learnt is encompassed in
theme 1: implicit messages about well-being. Theme 2: well-being is not
prioritised, and theme 3, connection maintains well-being, provides insight into
what was learned. Finally, theme 4: feeling inadequately prepared for
postqualification life, addresses the impact of learning. A breakdown of the
number of contributing participants per theme is provided in Appendix P.

Well-being and Burnout in Psychologists 124
Figure 1
An overview of the emerging GETS organised by career stage, themes most relevant to the research questions are highlighted
Well
-
being
throughout training
Sources of Pressure
Barriers to Accessing Help
Gratitude for training
place
Personal Characteristics
Connections Maintains Well
-
being
Validation through
shared experience
with
cohort
Containment and
guidance from
supervisors
Implicit and Explicit messages about well
-
being
Important Factors in
managing well
-
being
Feeling inadequately prepared for post
-
qualification
life
Unlearning
messages
from training
Reducing Working Hours
Hours
Sources of Pressure
Unsupported and unheard by course
Increased
responsibility
Service
Pressures
Expectations
from others
Lack of
support
Not
feeling
Valued
Well
-
being
support felt
tokenistic
Choice of Job Role
Setting Boundaries
Training Lacked helpful
learning opportunities
Well
-
being
Post
-
Qualification
During
Training
Up and Down
Gradual Decline
Competing Demands
Constant Assessment
Expectations from
others
Well
-
being is not important / prioritised
Expectations to prioritise
workload over work
-
life balance
Training Requirements more
important than wellbeing

Theme 1: Implicit Messages about Well-being
A key theme in participants' well-being-related learning experience brings
attention to how participants learned. It captures the significance that
participants placed, within their ideographic sense-making, on the unspoken
aspects of communication. Several participants, including P4 and P11 (shown
below), used the word ‘implicit’ in their sense-making accounts, whilst others,
such as P7 described ‘unspoken rules’ that existed in the communication
between themselves and others.
Participants seemed to experience and make sense of these
communications and learning interactions as insidious, captured by descriptions
of the learning as ‘powerful’ (P2) whilst also being ‘just really unhelpful’ (P9). At
some point in their interview transcripts, all participants who contributed to this
theme referred to an interaction with an individual as an interaction with ‘the
course’. This highlighted a sense of ‘othering’ in how participants made sense of
the relationship between trainees and course staff.
For some participants, these implicit messages communicated a belief
that participants should not ‘complain’ about their well-being. There was a
sense that participants felt an expectation from course staff to be grateful for
their place on training.
P:4 ‘…yeah I think there's lots that the course has going for it in terms of
the funding [ …], but I think it does perpetuate this “you should be
grateful to be here” mentality. I really felt that that was an implicit
message that you shouldn't complain too much 'cause we're doing you a
favour by letting you be here and funding this course for you.’

For some participants, this expectation or culture of gratitude seemed to
cause frustration and was experienced as invalidating or in conflict with their
lived experience of clinical training.
P:11 ‘…I felt there was an implicit kind of message if you have to get on
with it, don't complain too much, and you are fortunate to be here; you're
lucky to have your place on your course with all this funding. Just be
quiet, get on with it and don't cause too much trouble.’
This participants sense-making of expectation to be grateful appears to
allude to a sense that these interactions discouraged them from speaking out
about their well-being experiences. Another participant described how implicit
messages were received about the acceptability of discussing well-being during
training.
P3: ‘…I made a comment along the lines of “sometimes I find it really
hard to separate the stuff that's happening for me in the room and the
anxiety of being a new trainee”,… and I remember the person that was
leading the session being like “, yeah and that's why it's really important
that you have the space to think about that”, and then just moving very
quickly on with something else. And I remember thinking, okay, so the
message is we're not talking about that now that's too much deal with it,
and then there was no check-in after.’
Participants connected with this aspect of their experience by sharing
specific examples of times they received implicit messages, quoting language,
describing their emotional response to the experience, and offering more
generalised learning or ‘rules’ about well-being that they took from the

experience. Participants did not distinguish between the messages learned from
their academic versus their NHS experiences. Though this might reflect the
interconnected nature of the clinical and academic aspects of training, it may
also suggest a homogeneity in participants’ experience of well-being cultures
across the different organisational subcultures.
Theme 2: Well-being is Not a Priority
Most participants reported not feeling their well-being was a priority
during clinical training. This deprioritisation appeared to be held by others, and
participants learned through interpersonal verbal and behavioural interactions
on training. This theme captured two distinct learned beliefs or assumptions
about well-being as experienced by participants.
Training requirements are more important than your well-being.
Half of the participants interviewed felt that the words and behaviours of
others communicated that the requirements of the DClinPsy were more
important than their well-being.
P6: ‘…I think that message implies, you know, maybe in a very unspoken
way, kind of, yeah, look after yourself. But first and foremost, make sure
you do everything you need to do to finish the course and kind of
everything else should get kicked to the side as long as you do the
course.’
There was also a learned sense from participants that others considered
well-being to be a ‘luxury’ (P10) not a necessity.

P:4 ‘…I think that probably emphasized again that you're here to do a job
that's what we're interested in is getting you through this course, and if
we can do that with you as a relatively functioning human at the end of it,
then that's great, but that's not essential.’
This quote suggests that some experienced a sense from course staff
that there was a split between the needs of participants as employees and their
emotional and well-being needs. Ultimately, this left them feeling that, from the
course perspective, their emotional well-being was considered less important
than their work responsibilities.
Another way in which participants described the de-prioritisation of
wellbeing was through the learned belief that they should ‘just keep pushing’
through normal limits for well-being. This learning happened through means
including discussions with ‘the course’, older cohorts, and local supervisors.
P4: ‘…I wonder if a bit of that came from the cohorts that went before us
as well, not necessarily in a negative way that more in a this is shit, but
you need to keep going, keep pushing on and we will support you if you
can.’
In conversing with other training cohorts, there was a sense of
participants experiencing the lack of consideration for wellbeing as an
inevitability that they ‘others have done it before me, and hundreds will get
through it after me […]That’s just the way it is’ (P11).
Expectations to prioritise workload over work-life balance Over half
of the participants experienced learning that there was an expectation for

them to work substantial additional unpaid hours on top of their contracted
working hours. Many participants described learning that their employer, in
this case, the NHS, expected them to work additional hours to complete their
job demands.
P:7 ‘…we had a very long reading list after every lecture.[…] That in itself
sets an expectation as to what you think people are going to be able to
achieve or how much time you think they should be spending in work on
top of the 9-5 day. Because I suppose if your 9-5 day is attending that
lecture, when do they suggest that you complete that reading?’
Some participants felt that there was no way to complete the course
requirements without working over their contracted hours and described feeling
pressured to complete their work at any cost.
P6: ‘That if you want to pass, if you want to get everything done by the
deadlines, which you need to do on the course, you ultimately have to
work all hours under the sun a lot of the time…’
For many participants, these beliefs that others expected them to work
additional hours and that this was required to complete their professional
responsibilities were generalised into their post-qualification beliefs about their
well-being.
P:6 ‘I almost carried that over into qualified life. So then I would be so
used to just working all the time. But if you got to five o'clock and I still
had the stuff to do up, you know yeah, sure like, and then I would just be
carrying on,’

This seemed to demonstrate how learned working practices during training
‘just rolled over’ (P4) into post-qualification, almost becoming the participant's
default way of working. One participant, however, acknowledged the expectation
to work additional hours but identified this as unhelpful and spoke of their ability
to boundary their behaviour around working hours once qualified.
P:10 ‘…I think these bad patterns get ingrained during training… I think
it’s completely damaging to well-being. I see it play out in my friends and
even on placement, and since qualifying friends will work on the
weekend to catch up on work or their logging onto their emails, and I’m
like absolutely not; no way you don’t pay me to do that I’m not doing it.’
The experience of a lack of boundaried working hours and practices
during training appeared to facilitate a move towards an increased rigidity in
terms of setting boundaries and how they applied their job description in their
post-qualification practice. For this participant, there was almost an oppositional
response to their training experience.
Theme 3: Connection Maintains Well-being
A central theme in participants' learning experiences was the connection
with others and the meaning that they placed on this connection.
Validation through shared experience with the cohort
The majority of participants expressed that their fellow trainees were an
essential source of support that ‘kept them going’ (P7) through training. There
was a general sense that participants would have felt unable to manage the
training process without having a ‘cohort of support’ (P2). Having a group of

peers experiencing the same or similar challenges was validating for
participants and formed an essential aspect of supportive cohort relationships.
P8: ‘…I think some of the kind of the nice things that that I kind of learned
was actually about that sense of kind of peer camaraderie, sort of
validation. I don't think - there are lots of things that are problematic, I
guess, about my training experience, but the one thing that wasn't was
the people I was training with and having that was such a massive
support system to me at the time.
For some participants, there was meaningful learning around the
importance of shared experience and how this is related to an increased
understanding from others which participants valued.
P: 7: ‘…I certainly learned the value of peers, and I think that's still
something that I draw on now post-qualification. I had a really good
group of friends within my trainee cohort, and we're still good friends
now, and I think that really showed me the value of being able to have
peers who are in a similar situation if not the same situation as you and
they have that sense of understanding that maybe your family or friends
don't have.’
Participants experience of support from their cohort led to them feeling
understood and validated their experience of distress during training, leaving
them to make sense of these relationships as a helpful tool in managing
wellbeing.

Feeling supported by supervisors
Support from local clinical and internal course supervisors was also
considered important learning in relation to maintaining well-being during
training. Some participants found that feeling well-supported enabled them to
feel more able or motivated to prioritise their well-being.
P10: ‘…I think the driving force that powered me to [prioritise my
wellbeing] was that I had a really good personal tutor supervisor; he was
very supportive..’
For others, supervisors were important in keeping them ‘focused on
getting through it and getting out the other side’ (P11)
P2: ‘…Luckily had a really, really good supervisor who just kept me on
the straight and narrow with it. That was really, really important for my
well-being.’
Others made sense of their learning experience by understanding
supportive relationships as being helpful in ‘navigating’ difficulties with
wellbeing.
P:4 ‘…My local supervisors were always very very good, one of my
supervisors was also my line manager through a lot of training as she was
always very supportive, and I could go to her with things. And she helped me
navigate some of those difficulties.’
When discussing supervision, some emphasis was placed on the
importance of relationships with local supervisors; participants' descriptions of
their experiences suggested that there was something meaningful about

supportive relationships with people who were slightly removed from the training
course itself.
Theme 4: Feeling Inadequately Prepared for Post-qualification Life
Regarding the impact of their learning experiences post-qualification, over
three-quarters of the participants reported that their experiences had left them
feeling unprepared to manage their well-being once they qualified.
Missed opportunities for learning about positive well-being management
Seven of the participants felt that clinical training did not prepare them for
the challenges to well-being they would face as qualified CPs. Participants
expressed a sense of missing out on opportunities for well-being-related
learning, which would have helped them better manage the post-qualification
period. Participants highlighted that they experienced training as focused on
passing the course rather than on ‘equipping us for what being a psychologist is
actually like (P8)’.
P: 7: ‘…my experiences of being on the course were that it was very
focused on meeting the competencies that you needed to meet and
completing the assignments that you needed to complete; I don't think
we were taught a lot about how to manage your own well-being and how
we can utilise self-care and how important advice all that is post
qualification.’
Two participants talked explicitly about the specific role of CPs in the
NHS workforce. They felt that training lacked opportunities to learn what is
expected of them within this role and how to be assertive when working in
complex NHS systems. One participant reflected on their experience of burnout

following training. One way they make sense of their experience is due to
missed opportunities to fully learn about the expectations of CPs in the NHS
workforce and how to advocate for themselves professionally.
P4: ‘…I think another thing that contributed to the burnout, which the
course could have prepared me for, but they didn't, was just knowing what the
role should look like. I have the impression that if I was going to my managers
and saying this is too much, I can't do this then that's me saying I can't do my
job because they wouldn't give me these things to do unless they thought that
was part of my job as a psychologist… The NHS is awkward and clunky, and it
doesn't always work, and I think you need to be able to point that out and stand
up for yourself within that, and that's really important for your well-being, and I
don't think the course really prepared, us for that at all.’
For many participants, including P4, there was a sense of feeling let
down and increased vulnerability in the newly qualified stage due to the missed
training opportunities and having to rely on others to outline what is and is not
expected of them in the workplace.
Counterproductive Learning Experiences
When detailing their ideographic learning experiences relating to
wellbeing during clinical training, several participants described holding onto
learned behaviours in their working practice that were unhelpful
postqualification.
P6: ‘…Yeah, I’m having to unpick a lot of things I learned about working
over, prioritising my own well-being, not wanting to disclose etc.’

Participants talked about different ways in which their learning had been
counterproductive, as described by P6 above; some were able to identify
specific pieces of learning which underpinned these working practices.
P8: ‘…It’s like training sets you up to ignore your own red flags that
things are too much because there’s just so much to do, and rather than
preparing you for post-qualified life, it becomes actively unhelpful.’
Here, P8 describes how they learned to ignore or dismiss signs that their
well-being was deteriorating because of a sense that their work demands took
priority. For many, a sense of frustration was caused by a felt experience that
they had to unlearn these working behaviours and beliefs instilled during clinical
training. Participants described this unlearning process as needing to take place
to better manage their well-being post-qualification.
For others, their learned response was not just about unpicking aspects
of their learning but more of an oppositional behavioural response to their
experience.
P: 10 ‘…I think, if anything, my experiences of well-being during training
has given me something- or have left me wanting to do the opposite of
what happened in training. So now, if there’s any suggestion about really
doing some work outside of hours, I’m like, no, absolutely not.’
Discussion
Maintaining well-being is important in preventing burnout and
occupational distress in CPs (Rupert & Dorocaik., 2019); however, historically,
CPs have struggled to acknowledge this importance (Wise et al., 2012). This
study explored CPs' experiences of learning about well-being through training

and the impact of this learning post-qualification. To the researcher's
knowledge, this study is the first to present findings related to this aspect of CPs
well-being experiences.
Using IPA, four group experiential themes were identified: implicit
messages about well-being, well-being is not a priority, connection maintains
well-being and feeling inadequately prepared for post-qualification life. The first
theme refers to how CPs learned. The following two focused on what CPs
learned. Whilst the remaining theme captures the experienced impact of CPs'
learning. A difference in the experience of well-being stressors during and after
training were also observed. Themes are discussed alongside relevant theory
and research.
How CPs Learn About Well-being
Implicit Messages about Well-being
Participants in this study described highly influential learning experiences
relating to well-being through the receipt of implicit messages from the course
staff. Often, these messages demonstrated beliefs held and communicated by
‘the course’ (a term used by all participants to refer to course staff as a
collective) about how CPs were expected to view their well-being and behave in
relation to their well-being management. Participants described these
messages as unhelpful, negatively impacting their lived experience of wellbeing
and what they learned about managing well-being. Underlying beliefs and
assumptions are indicators of OC which can often be unspoken and even
unconsciously held beliefs that individuals are unaware that they are holding
and communicating to others (McSherry & Pearce., 2018). The participants'

experiences in this study may represent deep and underlying manifestations of
the OC relating to well-being across DClinPsy training courses (Mannion &
Davies., 2018). Little is known about how CPs learn about well-being during
training; however, research acknowledges that clinical training programmes are
ineffective at equipping CPs to manage their well-being (Lambert & Simon,
2008). The findings suggest that a significant aspect of CPs' learning about
well-being occurs through communicating underlying cultural beliefs and
assumptions.
Participants' descriptions of their learning experiences support claims
that NHS working practices are heavily influenced by unspoken aspects of
organisational culture (OC) (Dixon-Woods et al., 2013); however, the reference
to course staff indicates that implicit messages are also part of the academic
culture which provides an early insight into the academic culture experiences by
trainee CPs. Consequently, the dual identity held by CPs as students and
practitioners may make them vulnerable to multiple OCs in their experience of
learning about well-being. This aspect of trainee CPs experience is yet to be
explored, but the literature would benefit from a deeper understanding of the
impact of holding dual status during clinical training. In the meantime, these
findings suggest that course providers should carefully consider the different
organisational influences when developing and delivering course competencies
relating to well-being.
For CPs in this study, learning about well-being was a complex
embodied experience, and relying solely on psychological discourse (such as
lectures) to address well-being during training may be insufficient to meet the

needs of CPs (Stolz., 2014). Embodied learning theories acknowledge the role
of the body and emotions in the learning process (Kontra et al., 2012) and are
regularly incorporated into primary, secondary and higher education
(Rodríguez-Jiménez & García-Merino., 2017; Schmidt et al., 2019). CPs often
spoke of their emotional responses to their well-being learning experiences,
thus, highlighting the importance of emotionally embodied learning opportunities
for trainee CPs. Embodied learning principles may be beneficial in supporting
and improving the well-being-related learning experiences of CPs during clinical
training.
Clinical psychology training is among the UK's most sought-after
postgraduate psychology programmes (Callahan et al., 2018). There are large
numbers of applicants for comparatively few funded places (Scior et al., 2014;
Demetri et al., 2023). As a result, there is a culture of intense competition
among prospective applicants (Smith., 2014). Through interactions with course
staff, participants experienced an expectation from others to be grateful for their
training place, which was dismissing of participants' lived experience of training.
The experiences discouraged participants from expressing distress relating to
course challenges. The application process has been shown to take an
emotional toll on aspiring CPs (Demetri et al., 2023); however, the research has
not explored the longer-term impact of the application process on CPs. The
findings of this study suggest that experiencing the highly competitive
application process may contribute to a culture of expected gratitude, which
may dismiss the well-being experiences and needs of trainee CPs.

What CPs Learn About Well-being
Well-being is Not a Priority
The importance of culture was apparent in how CPs learned about
wellbeing and what they learned. Like their medical colleagues (Rich et al.,
2016), CPs described learning that there was an expectation to subjugate their
wellbeing needs for their clinical training requirements. Traditionally, the JDRM
has relied on separate models and theories to understand the aspects of OC in
the experience of well-being (Lopez-Martin & Topa., 2019), such as subjugation,
as they are neither a demand nor a resource (Taris & Schaufeli., 2018). Often
the focus in supporting CPs to manage their well-being is to develop personal
resources (Pakenham & Stafford-Brown., 2012; Stafford-Brown & Pakenham.,
2012). This is evidenced in the BPS core competencies for psychologists, which
focus on developing strategies to '''handle' the emotional impact of their work
and the ability to monitor their fitness to practice (BPS., 2019, P.19). The
researchers argue that the demands and resources experienced by CPs are
rooted in the OC of their workplace (Dextras-Gauthier et al., 2012). By focusing
only on demands and resources, course providers risk over-attributing wellbeing
management to the individual and not acknowledging the wider environmental
impact (Slemp et al., 2015). Expanding the JDMR to include OC theories, as
recommended by Lopez-Martin & Topa (2019) could help to contextualise the
experiences of CPs and provide a greater understanding of the impact of NHS
working cultures. It also identifies OG as an area to target when developing
prevention and intervention strategies for supporting CPs wellbeing.

CPs in this study experienced expectations to work additional unpaid
hours, which is commonplace for NHS workers (Kim et al., 2018; Lawn et al.,
2020). CPs learned that the requirements of the training were more important
than their own well-being, which led to CPs subjugating their own needs. Much
like the wider NHS OC, this research provides evidence for an ongoing culture
of subjugation which is embedded during CPs clinical training.
Working additional hours can be a significant risk factor in developing
burnout (Lim et al., 2020). However, an interesting distinction exists between
the employer expectations of trainees and qualified CPs. It is generally
accepted that healthcare staff should not work outside their contracted hours
(Warner & Zaranko., 2020); however, this is not necessarily the case for
trainees. Trainee CPs are paid NHS employees who also complete a funded
academic qualification, which they can use to increase their professional
earnings, status, and responsibilities for the remainder of their careers (Clearing
House., 2023). Achieving a doctoral-level qualification is a demanding and
timeintensive process (Utami., 2019). Doctoral students across various
disciplines would be expected to work long hours to complete their studies.
Many students work full or part-time alongside their education to fund their
studies (Rowe., 2021). Therefore, the expectations on trainee CPs are not
unlike those placed on other doctoral or PhD students. Given the personal
benefits and the dual role of doctoral students, the expectation of completing
some of the academic components outside of work hours may be a reasonable
and realistic expectation for trainee CPs. From reviewing the application
information, however (Clearing House., 2013) the academic expectations
around working hours may not be emphasised clearly enough to prospective

applicants. Our findings highlighted that greater clarity and transparency from
clinical training courses around the dual role, and expectation of trainee CPs,
could be beneficial in managing the expectations of trainee CPs. Well-being
may be supported by setting clear expectations from the point of application
through to training itself.
Connection Maintains Well-being
Peer relationships have a positive impact on the well-being of healthcare
workers. Research has shown positive peer relationships can provide validation
(Viswanathan et al., 2020), and enhance coping strategies (Leng et al., 2021).
Participants in this study highlighted their supervisors and trainee colleagues as
being vital in managing their well-being throughout training. The shared
experience within peer relationships was particularly helpful as it provided
validation and an increased understanding of the nuances of training that family
and friends may not understand. Among healthcare workers, shared
experiences have been shown to improve well-being and decrease
occupational burnout (Kelsey et al., 2023). As such, this is a really important
finding supporting the potential benefit of encouraging peer relationships within
clinical training. As such, CPs should be supported and encouraged to form
meaningful relationships with their colleagues throughout; this could be
achieved through team building, reflective practice, and using compassionate
models to underpin team ethos.

The Impact of CPs Learning Post-Qualification
Feeling Unprepared for Post-qualification Life
Ultimately, for 10 participants, their training experiences left them feeling
unprepared to manage the challenges they faced post-qualification. Lambert & '
'Simon's (2008) claimed that clinical training courses fail to prepare CPs to
manage their well-being post-qualification, but they do not provide any insight
into why this might be. The participants' experiences in this study suggest that
CPs may feel unprepared for two reasons: missed opportunities for learning and
counterproductive learning experiences.
A substantial body of research details the complexity of NHS systems,
including its processes, pathways, and constantly changing economic and
legislative landscape (McKee., 2021). Participants described the challenges of
working in complex NHS systems and the lack of opportunities to develop
essential skills in assertiveness and boundary setting to help them navigate
this. The participants' commentary on their experiences of feeling unprepared
are concerning, given that the theoretical foundation of the competency-based
learning ethos, on which doctorate programmes are built, is to prepare trainees
more efficiently for clinical practice (Kenkel & Peterson., 2010). It highlights the
importance of adequate consideration and pre-qualification preparation for the
transition from trainee to CP and the associated challenges of the NHS context
to enable trainees to feel adequately prepared to manage their well-being.
Participants also reported that much of their learning experiences around well-
being during training were not helpful to their well-being post-qualification. The
difference in experienced job demands for trainee and qualified CPs indicates
that learning about well-being as a trainee might not be transferable to

managing the different pressures and expectations faced post-qualification.
According to Melesis's Transitionary Model as applied to student nurses, upon
qualification, there is a transition from the role of student to the qualified
practitioner (Melesis., 2010). Throughout this transition, the practitioners, in this
case, CPs, must learn to adjust to the new expectations and demands of their
qualified role (Wildermuth et al., 2020). It is common for practitioners who
transition from higher-level academic qualifications to feel overwhelmed by their
new job demands and feel unprepared (Unruh and Nooney., 2011). Additionally,
the change in responsibility may leave CPs feeling as though the well-being
strategies they learned during training do not meet their post-transition needs.
The level of social support, and guidance available from staff members during
the transitionary period, can significantly improve the success of the transition
period for student nurses (Meleis., 2010) and could be a helpful target for
interventions to support CPs’ well-being during the transition to post-
qualification.
One counterproductive learning experience described by participants
was learning to ‘to ignore your own red flags’ (P8), and they made sense of this
as being because there was ‘so much to do’(P8). By being encouraged to place
the job demands ahead of their well-being, participants learned to ignore signs
that their mental health and well-being were deteriorating. Once again, this
highlights that not only is the longstanding NHS culture of subjugation
(Mackenzie., 1995; McCarthy et al., 2020) a potential aspect of OC within the
DclinPsy training, but the findings provide an insight into how this is learned
during training, and the subsequent impact on well-being management. This

learned behaviour around ignoring signs of declining well-being may have
serious implications for CPs' well-being post-qualification and warrants further
investigation.
Ultimately, the findings of this study suggest that OC may negatively
impact CPs well-being-related learning experiences during training. Supportive
supervisory and peer relationships may play an important role in maintaining
CPs well-being pre- and post-qualification; however, the post-qualification
transitionary period for CPs can present challenges to well-being. The differing
experiences and expectations of trainees and qualified CPs may contribute to
the difficulties experienced during the training and transition period.
Implications and Recommendations for Clinical Psychology
Well-being beliefs and assumptions held by the DClinPsy community
may be shared, learned and maintained through implicit communication with
other community members, including course staff, different training cohorts, and
NHS placement providers. Findings suggest that training course providers may
benefit from focusing less on providing formal well-being learning opportunities,
such as lectures and workshops (Choi and Jacobs, 2011), and more on
identifying embodied experiential learning relating to well-being opportunities.
By examining (Panescu., 2021) underlying beliefs and assumptions about
wellbeing (Schein., 1998;) held by the different members of the DClinPsy
training community and how these are communicated to trainees throughout
their training DClinPsy courses may be able to improve CP's positive well-being
learning experiences.

Additionally, the interpretation of participants' lived experiences suggests
an expectation to subjugate one's well-being needs in place of role or course
demands is being communicated to CPs during training. This highlights an
identifiable behavioural feature of OC. Courses may benefit from exploring the
underlying beliefs relating to subjugation and how this is being communicated
through espoused values (Macfarlane et al., 2013), such as written
communication to CPs.
By engaging in the suggested explorations of OC, course providers may
be able to develop a greater sense of the well-being culture within the DClinPsy
and how this contributes to CPs' individual learning experiences as well as the
socially cohesive behaviour concerning well-being within clinical training and
post-qualified CPs (Macintosh & Doherty., 2008). Each of the 30 training
course providers will likely have distinct well-being cultures shaped by the host
university, local geographical and cultural influences and senior management
team. As such, each DclinPsy course should aim to individually explore the
beliefs and assumptions about well-being and how these manifest in their
DclinPsy training programme to help identify opportunities for meaningful
change (Mannion & Davies., 2018). Courses could do this by assigning
independent clinicians to complete observations and evaluations of all aspects
of the course, including the perspectives of course staff, clinical supervisors
and trainees, and providing a written report. This could be shared with existing
and previous DClinPsy community members for comment and used to generate
target areas for development. A brief literature review found no evidence of
explorations such as this in any other NHS training courses; as such, there is an

opportunity for DclinPsy courses to champion this type of exploration of OC and
well-being in professional training courses.
To draw upon the potential benefits of connection with others, training
providers and local NHS trusts should consider fostering supportive
relationships within teams, services and organisations. There are several ways
in which teams may choose to do this; Schwartz Rounds provide structures
forums for staff across all levels of an organisation to connect over shared
experiences regarding the emotional impact of their work (Flanegan et al.,
2020), which peer support groups specifically for trainee CPs and newly
qualifies CPs may provide safe spaces free of fear of assessment or appraisal
from senior staff (Ooi., 2019). DclinPsy courses may benefit from encouraging
the development of a clan-based culture where all members of the DclinPsy
community are encouraged to value and foster kinship, mentoring, teamwork
and collaboration (Cameron et al., 2022).
This research suggests room for improvement in the experience of
learning about well-being for CPs. To maximise learning opportunities during
training, the researchers propose adding a tenth core competency to the BPS
framework (BPS., 2019), called ‘Personal and Professional Well-being’. This
competency would focus on developing personal resources, awareness of
organisational culture theories and research, ability to observe and critically
assess organisational cultures, reflection on their well-being learning
experiences, fostering a connection with others, and preparing for the transition
to post-qualification. Incorporating this into the core competencies framework
means that course providers would be audited and regulated on the

effectiveness of this aspect of their course provision as part of the
reaccreditation process.
Limitations
Interpretive Phenomenological Analysis
The researcher's position as a trainee CP will have shaped the design,
data collection, development, and interpretation of the findings (Smith et al.,
2022). As detailed above and in the supporting appendices, the researcher took
several steps to minimise the risk of bias and ensure that the researcher
remained committed to an iterative approach to GET development, being led by
the data at all times. The researcher has endeavoured to provide a high level of
transparency concerning reflexivity, rigour and credibility, enabling the reader to
determine the study's quality and credibility. Though this is a fundamental
aspect of IPA, the researcher acknowledges that their relationship to the
phenomenon of interest increases the risk of researcher bias in the analysis
and interpretation.
Population and Sample
The population sample was small, and there was a lack of diversity,
particularly regarding gender and race. A robust justification exists for a smaller
sample within the IPA methodology (Smith et al., 2021). The aim here was to
explore the lived experiences of a small homogenous group and generate
findings that, when applied tentatively, could be meaningful to a larger,
appropriately homogenous group. The lack of diversity, however, is important as
it reflects the lack of diversity in the wider clinical psychology field (Callahan et
al., 2018). Future research would benefit from greater gender diversity, whilst

similar explorations could focus specifically on the experiences of people from
UK minority groups, typically underrepresented in clinical psychology (Dimmick
& Callahan., 2022).
Due to the volunteer sample, there is likely to be a sampling bias here,
as participants likely chose to participate because they had an invested interest
in well-being due to their lived experiences (Tiit et al., 2021). This is likely to
impact the sample's representativeness.
Contextual Demographic Information
Researchers did not ask participants to disclose which DClinPsy course
they completed. As a result, findings could not be discussed in the context of
the individual’s training course. Opportunities for considering divergence and
convergence of themes, such as experiences of connection for those with larger
versus smaller cohorts, were missed. Given how many clinical psychologists go
on to work on or in conjunction with training providers, the decision not to record
training institutions felt more aligned with the principles of IPA in enabling
participants to share their lived experiences and meaning-making organically.
Expansion of DClinPsy Training
In 2021, Higher Education England to increase UK training places for
CPs by 25% (Bawa et al., 2021). As a result, course providers have been
tasked with supporting more trainees than ever without significant increases in
resources or NHS capacity to provide placements. Unfortunately, as these
changes are relatively recent, there is a lack of research or anecdotal accounts
that explore the impact of the expansion of courses on the experience of
trainees. As this research is the first to explore CP’s well-being learning

experiences during training, researchers cannot comment on the impact of the
expansion of DClinPsy courses on the well-being learning experiences captured
in this study.
Further Research
Findings indicate that a more focused exploration of the role of implicit
communication in well-being learning across DclinPsy courses may be
beneficial. Researchers may wish to consider discourse analysis which can
facilitate an exploration of how language is used in conversations relating to
well-being and support a larger sample size (Paltridge., 2021). Researchers
should consider multiple perspectives in their exploration of DClinPsy culture
and well-being. Thus, qualitative explorations from the perspective of Clinical
Psychology doctorate staff, who hold a different hierarchical position to trainees
(Ovseiko & Buchan., 2012) may also provide insight into the learning culture
relating to well-being.
Participants experienced feeling unprepared for post-qualification. The
field may benefit from a large-scale quantitative study exploring clinical
psychologists' transition from pre to post-qualification. Researchers may wish to
use a transition theory adapted for healthcare training, such as the one posed
by Meleis (2010), as a theoretical basis for the enquiry. As this would be the first
study of its kind, a broader exploration of the transition process, with some
space for more specific enquiry related to preparedness, may benefit. This may
provide a greater understanding of CP’s transition into post-qualification, inform
the clinical psychology training process and provide guidance for supporting the

transition, as has been demonstrated by research relating to nurses (Kumaran
& Carney., 2014).
Conclusion
This IPA study aimed to explore CPs well-being related to learning
experiences during clinical training and the impact of this post-qualification. This
study found that much of CPs learning occurs through implicit communication of
underlying beliefs and assumptions about well-being between CPs and
DClinPsy course staff. Participants' experiences highlighted a well-being culture
in which individuals learned that well-being is considered to be less important
than job demands and where many CPs feel pressure to work unpaid hours.
Participants found validation and support in their relationships with peers and
supervisors which appeared to support individual experience of well-being. The
well-being learning experiences during training left many participants feeling
unprepared for the challenges of post-qualification work and in a position where
they felt less equipped or able to notice signs that their well-being needed
attending to.
The analysis demonstrates that an increased focus on understanding
and exploring the underlying beliefs within and across DclinPsy course
providers may be beneficial in understanding how to make meaningful changes
in the well-being and learning experiences of CPs. By including well-being as a
core competency DclinPsy courses may be able to provide a structure within
which they can better equip CPs for long-term careers in the NHS. Individual
course audits exploring different manifestations of well-being culture across the
DClinPsy provision may help to generate evidence to support culture change.


