


Emotional, Temporal, and Spatial Multisensory Integration and
Crossmodal Recalibration in Individuals with Psychosis
Proneness or Psychosis
Introduction
It has been discussed that psychosis, a severe mental syndrome characterized by
distressing symptoms such as hallucinations and delusions (American Psychiatric Association,
2022), might partly be rooted in marked alterations in sensory processing and perception (e.g.
Mettler, 1955; Uhlhaas & Mishara, 2006). Starting in the second half of the 20th century up
until today, research on perceptual impairments in psychosis has mainly focused on changes
within one sensory modality, revealing impaired sensory processing of
e.g. visual or auditory information (e.g. Javitt, 2009a, 2009b; Javitt & Freedman, 2015).
However, in everyday life information usually is perceived via multiple sensory modalities
and these so-called crossmodal stimuli interact with each other (Koelewijn et al., 2010).
Research interest in sensory processing of crossmodal information in psychosis has increased
over the last 20 years. It has been discussed that dysfunctional processing and integration of
crossmodal stimuli might reflect a key impairment driving perceptual deficits in psychosis,
facilitating distorted or confusing perception of the self and the world as well as potentially
contributing to the development of psychotic symptoms (de Jong et al., 2009; Postmes et al.,
2014; Tseng et al., 2015).
In this dissertation project, we investigated multisensory processing in psychosis. This
projects aimed to pursue the questions, which aspects of multisensory processing might be
impaired in psychosis and how these impairments might be associated with the development
of psychotic symptoms. In the following, I will first briefly discuss previous literature on
sensory processing in psychosis and then introduce multisensory processes and their basic
principles and function. After the short introduction of these two research fields, I will transfer
to the topic of this dissertation, discuss the literature on multisensory processes in psychosis
and reveal open research questions, which were experimentally investigated within the scope
of this dissertation project.
1 Psychosis and Sensory Processing
Psychosis is a severe mental syndrome affecting about 0.4% (12-month prevalence) of
the population (Moreno-Küstner et al., 2018). Psychotic disorders such as schizophrenia have

been rated among the worldwide top 15 disability causes (Vos et al., 2017). Patients with the
diagnosis of a psychotic disorder suffer from changes in e.g. cognitive, affective, and social
functioning severely affecting their everyday life and mental well-being (American
Psychiatric Association, 2022). Psychotic symptoms such as hallucinations and delusions
cause significant distress for patients and often occur in psychotic disorders such as
schizophrenia or schizoaffective disorder, but can also develop in affective disorders
(American Psychiatric Association, 2022; Gaebel & Zielasek, 2015).
It has been observed that psychotic symptoms do not only occur in patients with the
diagnosis of a psychotic disorder. Previous studies reported that they also occur in the general
population in reduced intensity and/or frequency as well as in stages prior to disorder onset,
i.e. in psychosis proneness (for a review, see Verdoux & van Os, 2002). Based on these
observations, it has been discussed that psychosis as a mental syndrome might not reflect a
dichotomous category, i.e. being either present or not, but might rather constitute a
dimensional phenomenon. This so-called continuum hypothesis of psychosis proposed that
psychotic symptoms occur on a symptomatic dimension from no psychosis to full-blown
psychosis (Verdoux & van Os, 2002).
Already about 70 years ago, Mettler (1955) proposed that distorted perception might
underlie the severe dysfunctions in cognition and emotional processes characterizing
psychosis. Subjective reports of patients with the diagnosis of a psychotic disorder often
described how they perceived the self and the environment to be altered and how this led to
confusion and distress (e.g. Javitt & Freedman, 2015; McGhie & Chapman, 1961). Intuitively,
one might think of psychosis as a disorder of perception since characteristic symptoms of
psychosis such as hallucinations reflect erroneous perceptual experience and hence suggest
dysfunctions in sensory processes (Wallace & Stevenson, 2014). Thus, psychosis might be
partly described as a disorder of altered perception and cognition, in which impaired
processing of sensory information drastically impacts the experience and interpretation of the
surrounding world and the self in it.
Previous research on sensory processes in psychosis mainly focused on processing of
visual or auditory information. Earlier studies reported numerous impairments in sensory
processing and perception such as sensory gating dysfunctions, impaired sound detection and
discrimination, deficient facial emotion recognition or reduced sensitivity to moving or
ambiguous visual information (for reviews, see e.g. Bob et al., 2014; Javitt & Freedman,

2015). It has been discussed that deficient sensory processing might play a pivotal role in
influencing cognitive functioning in psychosis in a bottom-up driven way. For example, a
deficit in tone discrimination observed in psychosis might lead to impaired speech processing
and emotional prosody recognition, thus exacerbating interpersonal difficulties (for a review,
see Javitt, 2009a). This approach suggests a link between dysfunctional perception and
higher-order cognitive impairments characterizing psychosis.
Beyond reports on impaired information processing in terms of dysfunctional
perception in psychosis (Javitt & Freedman, 2015), it has been discussed that psychotic
disorders might also been described as a disorder of cognitive disintegration (Bob et al.,
2014). It has been reported that patients with the diagnosis of a psychotic disorder showed
deficits in integrating information processed in distributed brain areas, suggesting a
disconnectivity in neural functions essential for holistic information processing and
potentially facilitating fragmentation of consciousness and cognition (for a review, see e.g.
Bob et al., 2016).
While most of previous research on sensory processing in psychosis focused on vision
or audition individually (Javitt & Freedman, 2015), the perceptual system does not merely
rely on individual senses for sensory information processing. Rather, the brain needs to
simultaneously process and integrate stimuli conveyed via multiple senses in order to perceive
a coherent world and initiate appropriate behavior (e.g. de Jong et al., 2009). This
phenomenon is called multisensory processing. Multisensory processes at least partly rely on
unisensory processes, thus it is likely that deficient processing of unimodal information might
give rise to pronounced deficits in multisensory processes (Foxe & Molholm, 2009). Since
psychosis is associated both with impaired unisensory processing and perception as well as
disintegration of information processing (Bob et al., 2016; Javitt & Freedman, 2015), it can be
assumed that multisensory processes might be impaired in psychosis. This might potentially
entail detrimental consequences for holistic perception and for subsequent cognitive processes
as well as adaptive behavior.
2 Multisensory Processing & Perception
2.1 Multisensory Integration
MSI, i.e. the integration of stimuli conveyed via different sensory modalities such as
vision and audition, describes the process, in which crossmodal stimuli are combined to form
a new response differing from the individual cues (Stein et al., 2010). It has been discussed

that MSI might reflect a non-linear gain mechanism, in which the resulting response goes
beyond mere addition of the contributing sensory signals (e.g. Meredith & Stein, 1986;
Schroeder & Foxe, 2005). MSI has been observed in a multitude of modality combinations
such as AV, audio-tactile, visuo-tactile or sensorimotor information, including stimuli of
various complexity such as simple flashes and sinusoidal sounds, stimuli with emotional
content or speech stimuli (Murray et al., 2016; Wallace et al., 2020).
Several features of crossmodal stimuli influence the likelihood of integration. The
integration of crossmodal stimuli is more likely when they are temporally and spatially
aligned or congruent in supramodal features like semantic or affective meaning (Collignon et
al., 2008; Doehrmann & Naumer, 2008; Meredith et al., 1987; Meredith & Stein, 1986; Stein
et al., 1989). The integration of crossmodal stimuli has been found to hold crossmodal gain
effects, i.e. neural and behavioural benefits, compared to processing of unimodal cues alone.
This phenomenon is called congruency facilitation and can be measured by higher detection
rates and faster response times when stimuli are congruent (Miller, 1982; Schroger &
Widmann, 1998). Moreover, incongruency of crossmodal information is associated with e.g.
lower detection rates, slower responses and higher error rates, called incongruency
interference (Welch & Warren, 1980). Furthermore, it has been observed that crossmodal gain
is greater for less effective, e.g. noisy or ambiguous, contributing unimodal signals. This
principle is called inverse effectiveness (Meredith & Stein, 1986).
Thus, it is beneficial to appropriately integrate crossmodal information in order to
optimize perceptual processes and subsequent cognition, e.g. through improving performance
under noisy sensory conditions (Meredith & Stein, 1986; Miller, 1982; Schroger & Widmann,
1998). However, given the constant overflow of incoming information, the perceptual system
is faced with the problem to decide when to integrate crossmodal stimuli and when not. This
means that the brain has to constantly infer which crossmodal stimuli belong to the same and
which to different events. It has been discussed that the brain solves this so-called causal
inference problem by means of Bayesian inferencing. Within this process, prior knowledge
about the association of crossmodal stimuli is combined with the sensory input stemming
from the respective signals to infer if it is more likely that crossmodal stimuli stem from the
same or different sources (Körding et al., 2007; Sato et al., 2007; Shams & Beierholm, 2010).
MSI can be experimentally investigated by means of various experimental paradigms.
For example, the ventriloquist effect (VE) describes the crossmodal capture of a sound

stimulus by a concurrently presented visual stimulus, which shifts the perceived location of
the sound in direction of the visual stimulus position (Alais & Burr, 2004; Radeau &
Bertelson, 1974). The McGurk effect, which is discussed to reflect linguistic MSI, describes
the fusion of incongruent AV syllables into the perception of a third syllable, which differs
from the visual and auditory cues (McGurk & MacDonald, 1976). In the temporal domain, the
double-flash illusion describes the illusionary percept of two visual stimuli when one visual
stimulus is presented temporally close to two sound stimuli (Shams et al., 2002). These
examples of multisensory effects are well suited to experimentally investigate MSI in the
laboratory. Further, they illustrate how crossmodal stimuli influence each other during MSI,
resulting in a response differing from the individual unimodal responses.
MSI has been discussed to be linked to the development of higher order cognitive skills,
e.g. selective attention, association learning, language acquisition, rule learning and affect
discrimination (Wallace et al., 2020). Thus, the intact development of multisensory processes
might be crucial for the maturation of several cognitive processes and skills (Murray et al.,
2016; Wallace et al., 2020). In sum, MSI constitutes a central process for the perceptual
system to order the multitude of incoming sensory information and its functioning is essential
for higher-order cognition, adaptive behavior, and for the creation of holistic percepts of the
environment and the self (Murray et al., 2016; Wallace et al., 2020).
2.2 Crossmodal Recalibration
Beyond the on-line integration of crossmodal information, the perceptual system is
able to adapt to changes in crossmodal characteristics. This so-called crossmodal recalibration
has been observed both in the temporal and the spatial domain, reflecting adaptations to shifts
in crossmodal features such as spatial disparity or temporal asynchrony (for a review, see
Chen & Vroomen, 2013). For example, repeated exposure to an AV temporal asynchrony
shifts the perceived simultaneity of subsequent AV stimuli in the direction of the previous
temporal AV conflict (Fujisaki et al., 2004; Vroomen et al., 2004). In the spatial domain,
exposure to an AV spatial disparity influences the perceived stimulus position of a
subsequently presented sound. Even after crossmodal exposure, the shift of perceived sound
position towards the previously presented visual stimulus persists when the subject is asked to
localize the sound without any visual stimulus present, an effect called ventriloquist aftereffect
(VAE; Radeau & Bertelson, 1974). These crossmodal temporal and spatial recalibration
processes have been discussed to reflect crossmodal learning mechanisms. It has been
discussed that the perceptual system adapts to a constantly changing world in order reduce

discrepancy between the senses and thereby maintains coherent and stable representations of
the environment and the self (Chen & Vroomen, 2013).
2.3 Potential Consequences of Impaired Multisensory Processes
In sum, MSI and crossmodal recalibration have been discussed to reflect processes
essential for ordering an environment overflowing with sensory input and for the creation as
well as maintenance of holistic and stable percepts of the world and the self (Chen &
Vroomen, 2013; Murray et al., 2016). This seems to be important for the development of
higher order cognitive skills (Wallace et al., 2020). Thus, it can be argued that dysfunctions in
multisensory processes might hold detrimental consequences for perception, cognition and
behaviour. For example, it could be hypothesized that dysfunctional MSI leads to impaired
integration of crossmodal stimuli and thus to reduced crossmodal gain or fragmentation of
sensory information stemming from the same event. On the other hand, excessive MSI
potentially leads to inaccurate binding of information, which did not originate from the same
event. This might result in confusing percepts or the learning of erroneous associations
(Odegaard & Shams, 2017). It has been discussed that such dysfunctions in MSI might be at
the root of aberrant perceptual experiences in psychosis, leading to fragmented and
unstructured perception of the environment and the self and potentially even facilitating the
development of psychotic symptoms such as hallucinations or self-disorders (Postmes et al.,
2014; Uhlhaas & Mishara, 2006).
3 Multisensory Processing in Psychosis
3.1 Previous Evidence on MSI in Psychosis
Comparing previous results on MSI in psychosis remains difficult due to a multitude of
different experimental methods such as varying targeted sensory modalities, experimental
paradigms or stimulus complexity and content (for reviews, see Tseng et al., 2015; Wallace et
al., 2020). To date, it is not sufficiently clear, which exact multisensory processes might be
impaired, if impairments might manifest as deficient or excessive integration or how impaired
MSI might express across various sensory modalities. Thus, the generalizability of findings on
MSI in psychosis so far is still limited, reducing the possibility to infer how globally MSI
might be impaired in patients with the diagnosis of a psychotic disorder. In order to get an
overview over the extent of dysfunctions in multisensory processes in psychosis, in the
following prior evidence will be briefly reviewed separately for each investigated domain, i.e.
temporal, spatial, linguistic, emotional or sensorimotor processing.

One domain of MSI, in which deficient MSI has been quite consistently observed in
psychosis, is the temporal domain. Several studies reported dysfunctional temporal MSI in
psychosis, with patients with the diagnosis of a psychotic disorder showing an enlarged
tolerance for crossmodal asynchronies during SJ or an impaired ability to judge the temporal
order of crossmodal stimuli (for a review and meta-analysis, see Zhou et al., 2018). It has
been discussed that these impairments might facilitate erroneous binding and deficient
temporal structuring of crossmodal information, resulting in confusing percepts (Amadeo et
al., 2022; Zhou et al., 2018). Further, such dysfunctions in temporal MSI have also been
reported in psychosis proneness (e.g. Di Cosmo et al., 2021; Marsicano et al., 2022) and it has
been hypothesized that deficient temporal MSI might facilitate the development of psychotic
symptoms (Amadeo et al., 2022).
In contrast, the spatial domain has received significantly less scientific attention. Only
few studies on spatial MSI in psychosis have been published and their results suggested that
spatial MSI might be unimpaired in psychosis (Tseng et al., 2015). However, comparability of
their findings might be limited due to variations in experimental designs as well as targeted
sensory modalities. Moreover, one of the most extensively researched operationalizations of
spatial MSI as implemented by a VE paradigm using simple AV stimuli (Bruns, 2019) has
been investigated in psychosis in only one of those earlier studies (de Gelder et al., 2003).
Studying basic multisensory processes in psychosis, i.e. in simple stimuli beyond the
temporal or spatial domain, might be helpful in evaluating the generalizability of
dysfunctional MSI in psychosis. Findings on basic multisensory processes in psychosis so far
have been rather inconsistent. Two previous AV target detection studies reporting conflicting
findings, with Williams et al. (2010) observing reduced crossmodal gain in patients with the
diagnosis of a psychotic disorder compared to controls, i.e. less benefit in AV compared to
unimodal trials, whereas Wynn et al. (2014) reported comparable AV target detection
performance in patients and controls. However, a recent visuo-tactile target detection study
observed typical crossmodal target detection in patients with the diagnosis of a psychotic
disorder (Moran et al., 2021), corroborating the findings of Wynn et al. (2014).
In domains with more complex stimuli such as stimuli with socially relevant content,
the picture so far is not sufficiently clear. On the one hand, patients with the diagnosis of a
psychotic disorder consistently showed deficient MSI in the linguistic domain compared to
healthy controls in previous studies. For example, results of previous studies indicated a

significantly reduced susceptibility to the McGurk effect or reduced crossmodal gain in AV
lip-reading paradigms during crossmodal compared to unimodal trials in patients compared to
controls (for a review, see Tseng et al., 2015). On the other hand, previous findings on MSI of
emotional information so far have been inconsistent, with reports on deficient, excessive as
well as intact integration of crossmodal affective stimuli (for reviews, see Lin et al., 2020;
Tseng et al., 2015). Nevertheless, Lin et al. (2020) and Tseng et al. (2015) proposed that the
inconsistency of findings on emotional MSI in psychosis might be largely attributable to
methodological differences in previous studies. Further, unisensory emotion processing
deficits are well documented in psychosis (D. Martin et al., 2020; Seo et al., 2020; Tripoli et
al., 2022; van Donkersgoed et al., 2015), so it could be argued that emotional multisensory
processes might also be impaired in psychosis. Thus, Lin et al. (2020) and Tseng et al. (2015)
assumed that emotional MSI – analogue to linguistic MSI – might show pronounced deficits
compared to multisensory processes involving simple stimuli (Tseng et al., 2015). This might
suggest selective impairments during processing of socially relevant crossmodal information
in psychosis, potentially contributing to interpersonal difficulties in individuals with the
diagnosis of a psychotic disorder (Lin et al., 2020; Tseng et al., 2015).
In the sensorimotor domain, i.e. stimuli including proprioception, multisensory
processes have been quite consistently found to be impaired in psychosis. For example,
patients with the diagnosis of a psychotic disorder showed an increased susceptibility to the
rubber hand illusion (Noel, Cascio, et al., 2017). This sensorimotor illusion describes the
effect that simultaneous tactile stimulation of a visible rubber hand and of the occluded own
hand leads to a proprioceptive shift, resulting in a sense of ownership over the rubber hand
(Botvinick & Cohen, 1998). Another example for dysfunctional sensorimotor processing in
psychosis can be found in impaired corollary discharge. In psychosis, a failure in the
appropriate integration of motor commands and the sensory consequences of one’s own
behaviour might lead to anomalous percepts of own actions. This might cause confusion about
the origin of own actions and facilitate psychotic symptoms linked to own behaviour (Bansal
et al., 2018; Thakkar et al., 2017). It has been discussed that previous findings on
sensorimotor processes in psychosis might indicate a weaker differentiation of the self and
external cues (Noel, Cascio, et al., 2017) and an impaired sense of agency over the own body
(Klaver & Dijkerman, 2016). Further, previous findings suggested that these dysfunctions
might be linked to psychotic symptoms such as delusions of control and hallucinations
(Bansal et al., 2018; Noel, Cascio, et al., 2017; Tschacher et al., 2017).

3.2 Crossmodal Recalibration in Psychosis
While there has been considerable work on MSI in psychosis, too little scientific
attention has been paid to crossmodal recalibration processes in psychosis. Published studies
on crossmodal spatial or temporal recalibration involving external, i.e. sensory-sensory stimuli
in psychosis are essentially non-existent. Thus, the extent to which crossmodal learning
processes might be associated with psychosis or if crossmodal recalibration might even play a
role in disorder development is poorly understood. It could be argued that impaired
crossmodal recalibration might lead to unstable and unreliable representations of the
environment and as such contribute to confusing and distorted perception previously reported
in psychosis (Javitt & Freedman, 2015; Uhlhaas & Mishara, 2006). In the sensorimotor
domain, previous evidence indicated that sensorimotor recalibration processes such as
visuomotor recalibration in tasks such as prism adaptation or saccadic adaptation might be
impaired in psychosis, suggesting deficits in perceptual motor learning processes (e.g.
Bartolomeo et al., 2020; Rösler et al., 2015). To date, the question however remains if
crossmodal learning, i.e. sensory-sensory recalibration might also be impaired in psychosis
and how this potentially contributes to altered perceptual experience in psychosis.
3.3 Interim Summary of Evidence on Multisensory Processes in Psychosis
In sum, findings on MSI in psychosis are rather heterogeneous and likely depend on
several factors such as stimulus complexity and targeted domain. Deficient multisensory
processes have been revealed in previous studies especially in the temporal, sensorimotor,
linguistic domain (Noel, Cascio, et al., 2017; Tseng et al., 2015; Zhou et al., 2018). Further,
alterations have also been observed in the emotional domain, albeit less consistently (Lin et
al., 2020; Tseng et al., 2015). A few previous studies indicated that MSI might be intact e.g. in
the spatial domain (Tseng et al., 2015), suggesting that multisensory processing might be
selectively impaired in more complex information such as social cues (Tseng et al., 2015) and
stimuli involving temporal and proprioceptive/sensorimotor signals (Noel, Cascio, et al.,
2017; Zhou et al., 2018). Due to inconsistencies in findings and/or limited number of
published studies, so far it however remains largely unanswered if deficits in MSI might
reflect a global deficit or are rather domain-specific. Further, to date it is unclear if deficits in
multisensory processing can primarily be observed in on-line integration processes or if they
extend to crossmodal recalibration. Previous findings on sensorimotor recalibration in patients
with the diagnosis of a psychotic disorder suggested deficits in perceptual motor learning (e.g.

Bartolomeo et al., 2020; Rösler et al., 2015). Studies are however needed, which investigate if
sensory-sensory recalibration deficits can be observed in psychosis.
Although it has been discussed that deficits in multisensory processes might be linked to
the development of psychosis (Tseng et al., 2015; Wallace & Stevenson, 2014), most of the
previous studies have administered cross-sectional designs in samples already diagnosed with
a psychotic disorder. However, to evaluate if dysfunctions in multisensory processing might
precede and potentially even play a role in disorder development or rather manifest as
consequence of disorder progress, it is crucial to investigate subjects with psychosis
proneness. So far, few studies on MSI in psychosis proneness have been published, and they
do not sufficiently cover the whole range of the above-mentioned domains of MSI.
Nonetheless, previous work suggested deficits in temporal MSI (Dalal et al., 2021; Di Cosmo
et al., 2021; Ferri et al., 2017, 2018; Marsicano et al., 2022) and sensorimotor processing
(Germine et al., 2013; Kállai et al., 2015; Torregrossa & Park, 2022) in psychosis proneness.
Findings on linguistic MSI in psychosis proneness have been inconclusive (Muller et al.,
2020, 2021). To our knowledge, no published study investigated spatial or emotional MSI in
psychosis proneness. This might especially surprise in the case of emotional MSI. Emotional
MSI can be assumed to be at least altered in psychosis and it has been discussed that deficient
emotional MSI might facilitate experiences of interpersonal difficulties (Lin et al., 2020;
Tseng et al., 2015). Further, impairments in unisensory emotional processing have repeatedly
been observed in psychosis proneness and a role in disorder development has been discussed
(D. Martin et al., 2020; Seo et al., 2020; Tripoli et al., 2022; van Donkersgoed et al., 2015).
Thus, studies on emotional MSI in psychosis proneness are necessary to gather support for
above-mentioned assumptions of its role in disorder development.
Taken together, while psychosis might at least partly be described as a disorder of
sensory processing and disintegration of information processing (Bob et al., 2014, 2016; Javitt
& Freedman, 2015), the picture on multisensory processing in psychosis is not yet clear
enough to pinpoint which exact processes are disturbed as opposed to those that remain intact.
Further, too little scientific attention has been paid to factors, which might influence
multisensory processing in psychosis. Moreover, it remains unclear if dysfunctions in
multisensory processes in psychosis might reflect a consequence of disorder manifestation or
if (potential) deficits in MSI and crossmodal recalibration might play a role in the
development of psychosis.

4 Linking Dysfunctional Multisensory Processing and the Development of Psychosis
4.1 A Lack of Theoretical Models on Multisensory Processes in Psychosis
Although previous studies assumed that dysfunctions in multisensory processes
facilitate the development of psychosis (e.g. Tseng et al., 2015), little attention has been paid
to revealing potential mechanisms, via which deficits in multisensory processes might
contribute to psychosis. It appears that previous research so far has been mainly driven by
research questions directly derived from experimental findings of preceding studies and less
based on models, which connect experimental findings and phenomenology of psychosis.
In their review, Postmes et al. (2014) proposed how self-disorders in psychosis, i.e.
deviations in the experience of the self, might be rooted in a deficit in the adequate processing
of proprioceptive and external cues. Dysfunctions in (multi)sensory processing, especially
sensorimotor and proprioceptive processes, give rise to uncertain and irritating perception. In
turn, the attentional focus shifts to internal processes such as thoughts and emotions, both
losing focus on sensory contextual and other meaningful information and increasing the focus
on potentially irrelevant details of internal processes. The authors hypothesized that this
process of impaired sensory input, attentional shift and subsequent deficient integration of
internal and external cues into a holistic percept occurs in a persistent cycle, leading to an
estranged experience of the self in the surrounding world. Further, they proposed that
psychotic symptoms can develop as a maladaptive mechanism to resolve or explain these
experiences by means of mental functions such as imagination or memory. Thus, sensory
conflicts and resulting confusing perception are resolved at the cost of reality monitoring
(Postmes et al., 2014).
Although the proposed account of Postmes et al. (2014) generated interesting
hypotheses on the potential role of (multi-)sensory processing in psychosis, their proposed
mechanism heavily focused on proprioceptive processes. Only very few published studies on
dysfunctions in sensory-sensory, i.e. non-proprioceptive processes in psychosis have been
considered in the account of Postmes et al. (2014). In this account, impairments in
sensorysensory processing have been largely neglected, subordinated into general sensory
impairments and as such were not sufficiently addressed as a potential key deficit driving
perceptual dysfunctions in psychosis, as it has been previously proposed (e.g. Tseng et al.,
2015). Moreover, Postmes et al. (2014) claimed that any sensory process, including the
processing of crossmodal information, is inevitably linked with interoceptive processes, with

the self serving as a reference for all sensory experiences (Postmes et al., 2014). It could be
argued that this claim might not strictly describe a sensory process per se but rather involve
cognitive, i.e. higher-order processes. This raises the question if the proposed mechanism by
(Postmes et al., 2014) coherently refers to sensory disintegration in terms of MSI or rather
disintegration between sensory processing and other mental processes. Further, while
(Postmes et al., 2014) discussed previous literature and a potential mechanism by which
altered (multi-)sensory processes might be linked to psychosis, they distinctly focus on self
disorders in psychosis. Hallucinations and delusions are only briefly mentioned in the
mechanism, if at all, limiting the explanatory value to an individual symptom of psychosis
rather than comprehensively addressing the syndrome of psychosis. Finally, despite the
proposition by Postmes et al. (2014) to explain the role of dysfunctions in multisensory
processing for psychosis, to our knowledge they did not elaborate a disorder model with
subsequent empirical testing of derived hypotheses.
To conclude, model accounts focusing on multisensory processing in psychosis and its
potential link to psychosis as a syndrome rather than isolated symptoms are lacking. Given at
least partly consistent reports of dysfunctional multisensory processes beyond sensorimotor
processes, i.e. in sensory-sensory processing (Lin et al., 2020; Tseng et al., 2015; Wallace et
al., 2020; Zhou et al., 2018), it is necessary to bring impaired sensory-sensory processing into
the focus of discussions on potential mechanisms of dysfunctional perception in the
development of psychosis.
4.2 Anomalous Perceptual Experiences as a Potential Link between Multisensory
Processing and Psychosis
To reconcile experimental findings on MSI in psychosis and phenomenology, it might
be fruitful to link experimental findings with previously published and empirically tested
disorder models of psychosis, which contain model components on perceptive processes. A
candidate for such a model is the cognitive disorder model by Garety et al. (2001; see
paragraphs below). Embedding evidence on associations between dysfunctional multisensory
processing and psychotic symptoms in a published disorder model will benefit the explanatory
value of the model and contribute to the understanding how altered (multi-) sensory
perception might impact the development of psychosis.
An extensive review of the published literature on multisensory processes in psychosis
revealed that previous studies directly examined correlations between experimental findings

and measures for psychotic symptoms such as the Positive and Negative Syndrome Scale
(PANSS; Kay et al., 1987) as opposed to investigating a potentially mediating construct. The
findings of these studies were largely inconsistent, with both reports on correlations (Castagna
et al., 2013; Ferri et al., 2014, 2017; Germine et al., 2013; He et al., 2021; Muller et al., 2021;
Müller et al., 2014; Portnova et al., 2021; Prikken et al., 2019; Sanfratello et al., 2018;
Stekelenburg et al., 2013; Stephen et al., 2013; Stevenson, Park, et al., 2017; Thakkar et al.,
2011; Torregrossa & Park, 2022; White et al., 2014; Williams et al., 2010; Wynn et al., 2014;
Zhou, Cui, et al., 2022) and no correlations (de Boer-Schellekens et al., 2014; Giannitelli et
al., 2015; Hanlon et al., 2016; Haß et al., 2017; Mangelinckx et al., 2017; B. Martin et al.,
2013; Pearl et al., 2009; Roa Romero, Keil, Balz, Gallinat, et al., 2016; Roa Romero, Keil,
Balz, Niedeggen, et al., 2016; Senkowski & Moran, 2022; Seubert, 2010; Stone et al., 2011,
2014; Surguladze et al., 2001; Vanes et al., 2016; Zhou et al., 2020, 2021; Zhou, Lai, et al.,
2022; Zvyagintsev et al., 2017) between MSI and psychotic symptoms. Further, about one
third of previous studies did not report any correlation analysis between their experimental
findings and symptom measures (de Gelder et al., 2003, 2005; de Jong et al., 2009, 2010;
Fiszdon & Bell, 2009; Liu et al., 2016; Moran et al., 2021; Noel et al., 2018; Ross et al., 2007;
Sestito et al., 2013; Simpson et al., 2013; Szycik et al., 2009, 2013; Thaler et al., 2013; Van
den Stock et al., 2011; Wroblewski et al., 2020; Zvyagintsev et al., 2013). It might be difficult
to directly relate experimental operationalizations of multisensory processes and
phenomenology of psychosis, with both reflecting distinct levels of psychological
observation. Thus, we aimed to explore a conceptual construct able to relate to both
components and thus to obtain first data for hypothesis generation on mechanisms linking
MSI and psychotic symptoms.
A phenomenological concept, which potentially links experimental findings and
psychotic symptoms, might lie in so-called anomalous perceptual experiences. Anomalous
perceptual experiences describe unusual sensory phenomena in all senses, such as perception
of unusually increased stimulus intensity or sensory experiences originating from an
inexplicable source (Bell et al., 2006; Wright et al., 2018). The concept of anomalous
perceptual experiences as operationalized by Bell et al. (2006) does not exclusively rely on a
clinical perspective. This is in contrast with earlier operationalizations of aberrant perception,
which often are biased towards clinical symptoms such as hallucinations rather than reflecting
a distinct phenomenon (Bell et al., 2006). Adopting the approach by Bell et al. (2006)
provides the opportunity to investigate perceptual anomalies both in clinical populations and

individuals from the general population with various degrees of psychotic experiences such as
persons with high psychosis proneness. Thus, this conceptualization of anomalous perceptual
experiences supports the continuum hypothesis of psychosis (Verdoux & van Os, 2002) and
enables the examination of altered perception separated of psychotic symptoms and as such of
altered perception in stages before psychotic symptoms manifest (Bell et al., 2006).
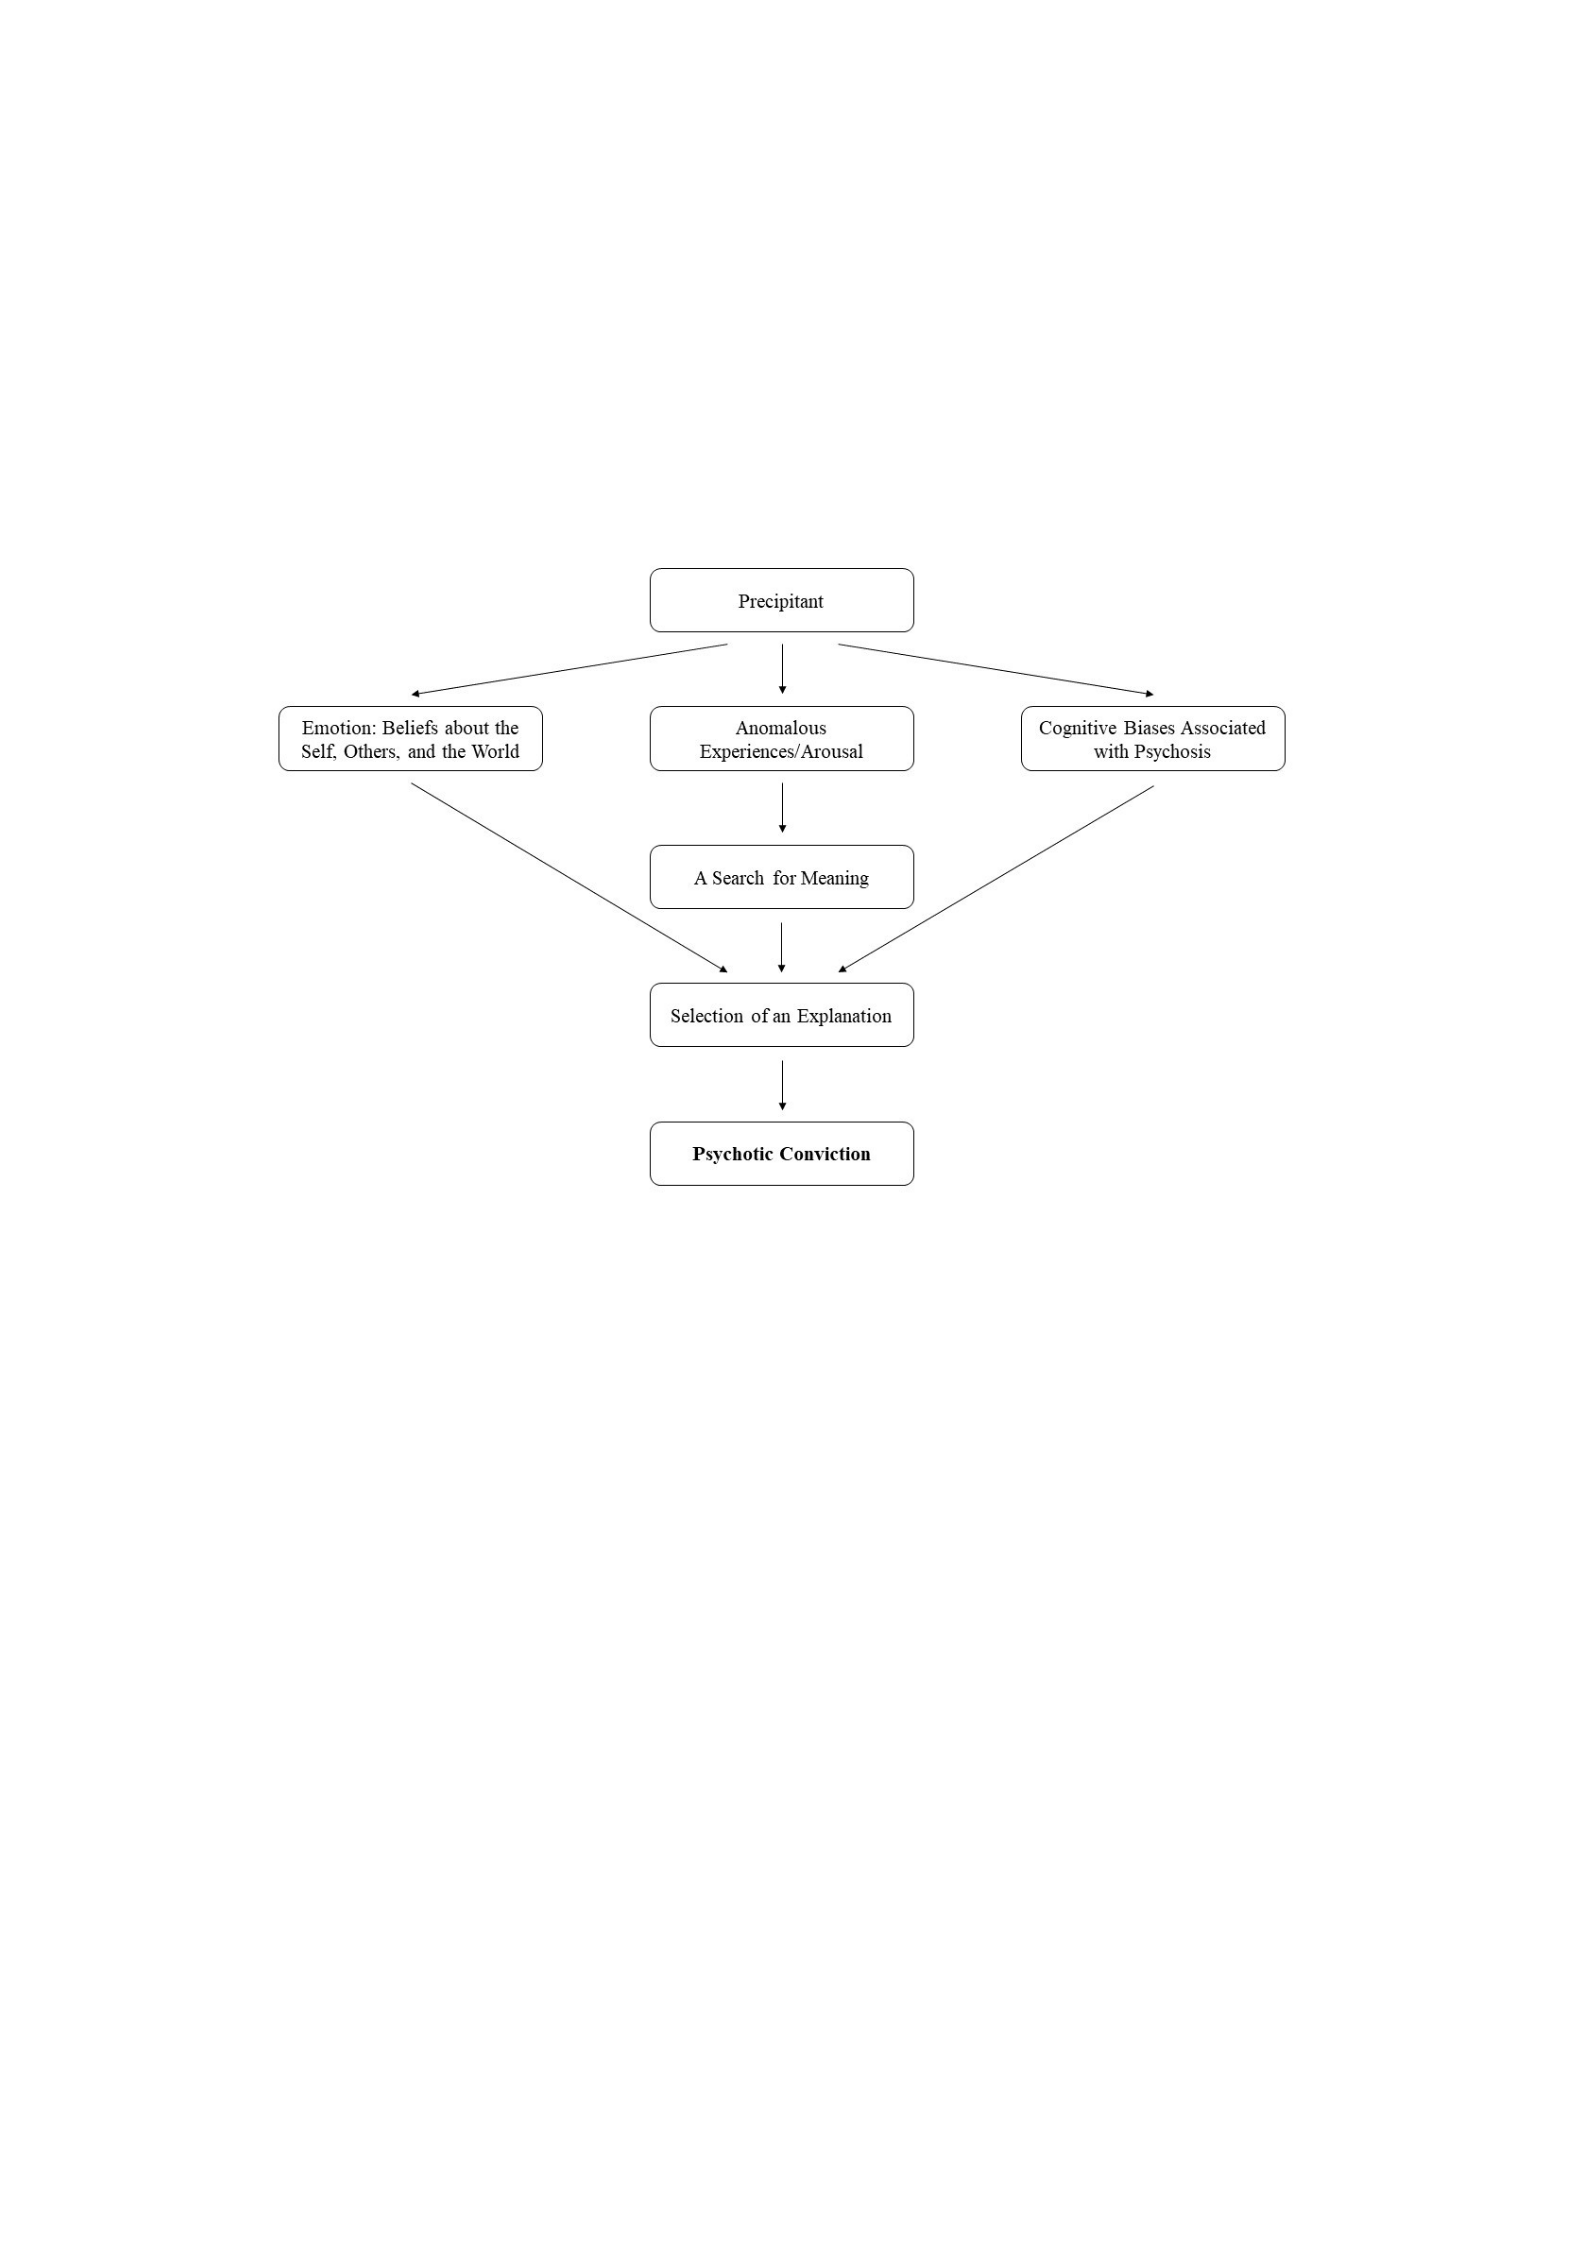
Aberrant perception in terms of anomalous perceptual experiences has been described
in the above-mentioned cognitive disorder model of psychosis by Garety et al. (2001). This
model incorporates aberrant perception as one key factor facilitating the development of
psychotic symptoms (see Figure 1 for a depiction of the model). Garety et al. (2001) proposed
that a stressful event can trigger a disruption of cognitive processes in individuals with a
predisposition for psychosis, leading to anomalous perceptual experiences such as hearing
one’s own thoughts aloud or distorted sensory input. These experiences are attentioncapturing,
irritating as well as arousing and demand the search for a cognitive explanation.
Confounded by cognitive biases such as the jumping-to-conclusion bias (Huq et al., 1988) and
negative beliefs about the self and the world, the interpretation of the anomalous experience is
biased towards negative, potentially threatening explanations and as such eventually facilitates
the construction of psychotic convictions (Garety et al., 2001).
While cognitive disorder model by Garety et al. (2001) introduced a mechanism how
aberrant perception might be linked to psychotic symptoms, the description what the
component anomalous perceptual experience entails might be rather vague and did not
address anomalous multisensory perception. In this dissertation project, we propose that
dysfunctions in multisensory processing, which lead to e.g. fragmentation of information
originating from the same event or erroneous binding of stimuli from separate sources, might
be associated with the emergence of conscious anomalous perceptual experiences. In this
perspective, dysfunctional multisensory perception might facilitate the manifestation of
psychotic symptoms in accordance to the mechanism described by Garety et al. (2001).
Following this approach might aid in addressing the above discussed question if impairments
in multisensory processes might play a role in the development of psychosis rather than
reflecting a consequence of disorder manifestation.
Thus, in order to generate hypotheses regarding anomalous perceptual experiences as a
potential conceptual link between experimental findings on deficient multisensory processing
in psychosis and psychotic symptoms, an additional aim of this dissertation project was to
investigate associations between measures of multisensory processes, anomalous perceptual
experiences as operationalized in the questionnaire Cardiff Anomalous Perception Scale
(CAPS) by Bell et al. (2006) and psychotic symptoms such as hallucinations and delusions.
Figure 1
Depiction of the Cognitive Disorder Model for Psychosis by Garety et al. (2001)
Note. The depicted path model was adapted from Freeman et al. (2002).
5 Summary of Open Questions
Within the scope of this dissertation project, four overarching open questions could be
derived from the literature on multisensory processing in psychosis and were subsequently
addresses in three experimental studies.
The first question followed previous discussions if dysfunctions in MSI in psychosis
could be observed on a global scope, suggesting a general underlying dysfunction, or might be
rather specific for certain domains of MSI (Tseng et al., 2015). As outlined above, previous
evidence rather tends to support the latter, but a lack of studies in spatial MSI and
inconsistencies of findings in emotional MSI in psychosis so far prevented clear conclusions.
Thus, we followed up on the first question “1: Are Multisensory Integration Deficits in
Psychosis Global or Domain-Specific?” by investigating both emotional and spatial MSI in
subjects with psychotic symptoms. We aimed to contribute to previous evidence on emotional
MSI in psychosis and to address the issue if emotional MSI might be deficient or excessive.

Further, we aimed to gather evidence on spatial MSI in psychosis, targeting the relative
scarcity of data in this field.
The second question addressed the lack of evidence on crossmodal learning in
psychosis. As discussed above, studies investigated sensory-sensory recalibration in psychosis
are lacking, whereas previous studies indicated deficits in sensorimotor recalibration
processes in psychosis (e.g. Bartolomeo et al., 2020; Rösler et al., 2015). We aimed to provide
first evidence on sensory-sensory recalibration in psychosis and by this address the question
“2: Is Crossmodal Learning Deficient in Psychosis?”. We experimentally examined
crossmodal temporal recalibration in patients with the diagnosis of a psychotic disorder and
by this investigated if impairments temporal MSI previously reported in psychosis (Zhou et
al., 2018) also extend to crossmodal temporal recalibration. Further, we investigated
crossmodal spatial recalibration in patients with the diagnosis of a psychotic disorder,
addressing the scarcity of findings on spatial multisensory processes in psychosis and
providing first evidence on crossmodal spatial recalibration.
The third question addressed the relative lack of studies on MSI in psychosis
proneness. This question followed up upon the above outlined discussion if impaired MSI
might contribute to the development of psychosis rather than reflecting a consequence of it
(Tseng et al., 2015). Most of previous research has been conducted in patients with the
diagnosis of a psychotic disorder and published studies in psychosis proneness did not
sufficiently target all domains of MSI. While studies have been conducted in the temporal
(Dalal et al., 2021; Di Cosmo et al., 2021; Ferri et al., 2017, 2018; Marsicano et al., 2022),
sensorimotor (Germine et al., 2013; Kállai et al., 2015; Torregrossa & Park, 2022), and
linguistic domains (Muller et al., 2020, 2021), none have been published in the spatial and
emotional domain. Given previous discussions of a potential role of dysfunctional emotional
MSI for the development of psychosis (Lin et al., 2020; Tseng et al., 2015) and consistent
reports of impaired unisensory emotion processing in psychosis proneness (D. Martin et al.,
2020; Seo et al., 2020; Tripoli et al., 2022; van Donkersgoed et al., 2015), we aimed to
contribute to the question “3: Are Deficits in Multisensory Processing in Psychosis a
Precedent or a Consequence of Disorder Development?” by investigating emotional MSI in
subjects with psychosis proneness.
The fourth and last question addressed in this dissertation project aimed to target the
lack of attempts to reveal mechanisms, which link dysfunctional multisensory processing and

the phenomenology of psychosis. As outlined above, we proposed the concept of anomalous
perceptual experiences described in the cognitive disorder model of psychosis by Garety et al.
(2001) as a potential mechanism linking experimental measures of multisensory processing in
psychosis and psychotic symptoms. This approach further contributed to the question if
dysfunctional multisensory processing might play a role in the development of psychosis by
providing initalevidence for a specific mechanism, via which multisensory processing might
contribute to psychosis. Thus in order to address the question “4: Can Anomalous Perceptual
Experiences Conceptually Link Multisensory Processing and Phenomenology of Psychosis?”,
we aimed to reveal potential associations between experimental findings on emotional,
temporal, and spatial multisensory processes in psychosis, anomalous perceptual experiences
as operationalized by the CAPS (Bell et al., 2006) and self-reports on psychotic symptoms. By
this, we aimed to gather evidence for future hypothesis generation regarding mechanisms
linking multisensory processing and psychotic symptoms.
6 Outlook on the Experimental Studies in this Dissertation Project
In order to investigate the questions outlined above, we conducted three
different studies covering various multisensory processes in individuals with different
levels of psychotic symptoms.
In our first study, which is addressed in Chapter II “Emotional Multisensory
Integration in Psychosis Proneness”, emotional MSI was investigated in psychosis
proneness administering a paradigm on AV emotion processing by Föcker et al. (2011). The
aim of this study was to investigate if findings on dysfunctional emotional MSI in individuals
with psychotic symptoms can be replicated and if emotional MSI might be already altered in
psychosis proneness. This study addressed questions 1 and 3 of the above outlined open
questions.
Chapter III “Temporal Multisensory Integration and Crossmodal Temporal
Recalibration in Psychosis” focuses on our second study on temporal multisensory
processing in psychosis. Temporal MSI and crossmodal temporal recalibration were
investigated in patients with the diagnosis of a psychotic disorder and healthy controls by
means of a paradigm adapted from Van der Burg et al. (2015). This study’s objective was to
both replicate earlier findings on impaired temporal MSI in psychosis and to provide first
evidence if dysfunctions in crossmodal temporal recalibration can be observed in adults with

the diagnosis of a psychotic disorder. This study aimed to contribute to questions 1 and 2 of
the outlined open questions.
Chapter IV “Spatial Multisensory Integration and Crossmodal Spatial
Recalibration in Psychosis” covers our third study on spatial multisensory processing in
psychosis. Both spatial MSI and crossmodal spatial recalibration were investigated in patients
with the diagnosis of a psychotic disorder and healthy controls with a paradigm on the VE and
VAE adopted from Bruns & Röder (2015). This study aimed to replicate earlier findings on
spatial MSI in psychosis and provide first experimental evidence on crossmodal spatial
recalibration in psychosis. The third study addressed questions 1 and 2 of the open questions.
To evaluate if dysfunctional MSI might be linked to the phenomenology of psychosis
via the mechanism of anomalous perceptual experiences, we investigated associations
between multisensory processing, anomalous perceptual experiences as operationalized by the
CAPS (Bell et al., 2006) and psychotic symptoms in all three studies. Based on the cognitive
disorder model of psychosis by Garety et al. (2001), we aimed to provide first evidence for
future hypothesis generation on a specific mechanism, via which impaired multisensory
processes might contribute to the development of psychosis. This approach addressed
question 4 of the outlined open questions.

19
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Chapter II:
Emotional Multisensory Integration in
Psychosis Proneness (Study 1)

20
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
1 Introduction
1.1 Multisensory Processing of Emotional Information
In our daily life, we constantly process social information to take part in society. Social
information can be verbal, such as spoken or written language, but also non-verbal, such as
emotional face expressions or vocal prosody. Most of the time, we perceive social cues via
multiple sensory modalities, which need to be adequately processed. For example, it is crucial
to adequately identify another person’s facial expression or vocal utterances in order to induce
appropriate reactions during social interactions.
Social information is often presented in noisy surroundings, e.g. in crowded spaces,
and comes with a high inter-individual ambivalence in terms of meaning and intent. In noisy
social situations, it is advantageous to process cues conveyed via multiple modalities for
recognition of social information. In line with the principle of inverse effectiveness (Meredith
& Stein, 1986), this crossmodal performance benefit increases when unimodal social stimuli
are highly noisy and ambivalent (e.g. Izen & Ciaramitaro, 2020; Tatz et al., 2021). This
highlights the importance of appropriate integration of crossmodal social cues for daily social
functioning.
Prior studies of emotional MSI in healthy subjects showed that emotion recognition
accuracy increased and response time decreased when emotional AV information was
presented emotionally congruent compared to unimodal stimuli. Presenting emotionally
incongruent AV stimuli lead to reduced recognition accuracy and higher reaction times (RT)
compared to unimodal stimuli (e.g. Collignon et al., 2008; Föcker et al., 2011). These
congruency facilitation and incongruency interference effects are thought to reflect emotional
MSI and seemed to be automatic and relatively independent of selective attention towards
either sensory modality (Collignon et al., 2008; Föcker et al., 2011; Föcker & Röder, 2019).
However, a recent study by Gao et al. (2021) found evidence for increased crossmodal
integration effects when participants were instructed to attend the auditory stimulus compared
to when attending the visual stimulus, which was discussed as suggesting a visual dominance
in AV emotion recognition. Crucially, modality dominance in multisensory processing is not
rigid and flexibly adapts to stimulus reliability. A general principle in multisensory processing
is that the more reliable modality dominates MSI. When the signal-to-noise ratio in the
usually dominant modality significantly decreased, the crossmodal impact of the usually

21
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
nondominant modality increased, eventually leading to a shift in modality dominance (e.g.
Alais & Burr, 2004; Collignon et al., 2008; Piwek et al., 2015).
1.2 Psychosis and Emotion Processing
In patients with the diagnosis of a psychotic disorder, deficits in social cognition are
well-documented (for reviews, see Healey et al., 2016; Savla et al., 2013). A large body of
studies on social cognition in psychosis investigated facial emotion recognition. These studies
indicated that the recognition of unimodally presented affective facial expressions was
deficient in patient samples (for reviews, see Barkl et al., 2014; Kohler et al., 2010), with
patients showing significantly lower recognition rates or mislabeling emotional content of
facial expressions compared to healthy controls (e.g. Darke et al., 2021; Tripoli et al., 2022).
Further, first-episode patients have been found to show neural hypoactivation towards
emotional face stimuli in neuroimaging studies, suggesting impaired neural processing of
affective information in psychosis (for a review, see Lukow et al., 2021). While not being as
extensively studied as facial emotion processing, several prior studies showed that processing
of unimodally presented emotional vocal prosody also was disturbed in patients with the
diagnosis of a psychotic disorder, with patients showing difficulties in identifying and
discriminating target emotions in vocal prosody (for reviews, see Gong et al., 2021; Lin et al.,
2018).
The magnitude of emotion processing deficits in psychosis might differ depending on
the specific target emotion (Barkl et al., 2014). Recent studies indicated that aberrances of
emotion processing in patients with the diagnosis of a psychotic disorder were more
pronounced for negative emotions compared to positive emotions, especially for fear and
anger (Tripoli et al., 2022; Won et al., 2019). Emotion processing aberrances were also present
with regard to affectively neutral information, with patients erroneously rating neutral face
expressions as having emotional content (Mitrovic et al., 2020). Compared to healthy
controls, affectively neutral information was rated as more intense in patient samples
(Dondaine et al., 2014) as well as mislabeled as negative more often in psychosis proneness
(Seo et al., 2020). Further, patients with the diagnosis of a psychotic disorder have shown
interference effects during emotion recognition, i.e. a tendency to confuse non-target emotions
with the target emotion (Dondaine et al., 2014), as well as a negativity bias, i.e. a tendency to
erroneously rate the target emotion as negatively valenced (e.g. Pinkham et al., 2011). In sum,

22
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
psychosis seems to be associated with especially negative-biased emotion processing deficits,
which might play a crucial role in experiencing psychotic symptoms. Supporting this
assumption, a recent study by Krkovic et al. (2020) revealed a predictive value of negative
emotions, especially fear, for persecutory ideation in both patients and subjects with psychosis
proneness. Further, experiencing negative emotions in turn also followed persecutory beliefs,
which suggests a vicious cycle between emotion processing and specific psychotic symptoms
(Krkovic et al., 2020). This highlights the potential detrimental effects of emotion processing
deficits, especially concerning the bias towards negative emotions, for individuals suffering
from psychosis.
Deficient processing of the emotional content of face or voice stimuli has been shown
to be associated with various psychotic symptoms like hallucinations and delusions, (Tseng et
al., 2013), as well as to be related to problems in social functioning (Brittain et al., 2010;
Pinkham et al., 2003). Further, Chapellier et al. (2022) recently showed that in stable
outpatients with the diagnosis of a psychotic disorder deficient processing of non-verbal social
cues was associated with impaired functional outcomes, such as engagement in everyday
activities and skills related to work or personal care, putting emphasis on the importance of
functional processing of social information for everyday life.
Impaired processing of affective facial expressions or vocal prosody have also been
identified in persons with high psychosis proneness (Seo et al., 2020; van Donkersgoed et al.,
2015) and first-degree relatives of patients with the diagnosis of a psychotic disorders (D.
Martin et al., 2020). In several studies, persons with high psychosis proneness showed
dysfunctional recognition and discrimination of affective facial expressions and vocal prosody
(for a review, see van Donkersgoed et al., 2015). Further, Seo et al. (2020) recently found a
negativity bias in facial expression recognition, i.e. a bias to rate neutral face expressions as
negative, as well as associations of impaired emotion recognition with higher scores in
schizotypy and paranoia in subjects with high psychosis proneness. Corcoran et al. (2015)
found that emotion recognition deficits have predictive value for the transition from high
proneness status to full-blown psychosis, suggesting a potential role of dysfunctional emotion
processing in the development of psychosis. Supporting this assumption, it has been discussed
that dysfunctional social information processing, such as facial or vocal emotion processing

23
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
deficits, might constitute a risk factor for the development of psychotic symptoms (D. Martin
et al., 2020; Seo et al., 2020; Tripoli et al., 2022; Tseng et al., 2016).
1.3 Psychosis and Emotional Multisensory Processing
While social cognition in terms of unisensory processing has been extensively studied
in psychosis, fewer studies have examined multisensory processing of social stimuli. Several
of these studies investigated processing of verbal social cues, i.e. crossmodal speech stimuli,
and consistently revealed impairments in MSI of verbal social cues in patients with the
diagnosis of a psychotic disorder (for a review, see Tseng et al., 2015). For example, studies
using the McGurk illusion (McGurk & MacDonald, 1976) indicated that patients show a
significantly reduced proportion of fused percepts compared to controls (de Gelder et al.,
2003; Pearl et al., 2009), suggesting impaired MSI of AV linguistic information in psychosis.
While linguistic MSI in psychosis has been consistently shown to be deficient in prior
studies, processing of arbitrary AV stimuli seemed to be rather intact. These findings might
reflect a pronounced deficit in processing crossmodal stimuli with a communicative value, i.e.
social stimuli, compared to non-social stimuli (Tseng et al., 2015). This suggests specific
difficulties regarding multisensory processing in social situations, with possible detrimental
effects on evaluating social encounters and potentially aggravating interpersonal problems in
psychosis (Tseng et al., 2015).
In contrast to consistent evidence of impaired MSI of verbal social cues in psychosis
(Tseng et al., 2015), empirical evidence regarding MSI of non-verbal social cues, i.e.
emotional stimuli, in psychosis has been rather inconsistent in previous studies (for reviews,
see Lin et al., 2020; Tseng et al., 2015). Compared to healthy controls, patient samples
showed either impaired MSI of emotional information (Castagna et al., 2013; de Gelder et al.,
2005, Exp.1; de Jong et al., 2009, 2010; Fiszdon & Bell, 2009; Jeong et al., 2021;
Mangelinckx et al., 2017; Portnova et al., 2021; Seubert, 2010), no group differences in
emotional MSI (Müller et al., 2014; Sestito et al., 2013; Simpson et al., 2013; Zvyagintsev et
al., 2013) or even an increased crossmodal influence during emotional MSI (de Gelder et al.,
2005, Exp.2; Van den Stock et al., 2011).
Multiple factors might have contributed to these inconsistent findings: varying levels
of symptom load and cognitive dysfunctions due to heterogeneous patient samples, potential
underlying unisensory processing deficits, aberrant attentional effects, differences in

24
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
experimental methods complicating comparability, or differences in target emotions or
modalities, (Lin et al., 2020; Tseng et al., 2015).
In line with the latter, de Gelder et al. (2005) found opposite group differences
between patients with the diagnosis of a psychotic disorder and healthy controls depending on
the task-relevant sensory modality: compared to healthy controls, patients showed a reduced
influence of vocal prosody on categorizing emotional facial expressions, while an excessive
influence of facial expressions on categorizing vocal prosody was found. de Gelder et al.
(2005) discuss their findings as suggesting an increased visual dominance during AV emotion
processing in patients with the diagnosis of a psychotic disorder. Supporting these findings,
Sestito et al. (2013) found that patients relied more on the visual than the auditory cue when
facial expressions and vocal prosody were emotionally incongruent. In contrast, other authors
presented findings of reduced crossmodal influence of emotional face expressions on judging
vocal prosody (de Jong et al., 2009) or an increased crossmodal influence of vocal prosody on
facial expression categorization (Van den Stock et al., 2011), suggesting an auditory
dominance effect in psychosis. In line with a potential auditory predominance, Thaler et al.
(2013) showed that patients with the diagnosis of a psychotic disorder showed a similar
positivity mislabeling bias in AV emotion recognition as in auditory only trials, while visual
trials were mislabeled more negatively-biased. In sum, while prior studies suggested visual
dominance during AV emotion recognition in healthy participants (Collignon et al., 2008;
Gao et al., 2021), findings on modality dominance in psychosis are inconsistent (Lin et al.,
2020; Tseng et al., 2015), supporting either visual dominance (de Gelder et al., 2005; Sestito
et al., 2013) or auditory dominance (de Jong et al., 2009; Thaler et al., 2013; Van den Stock et
al., 2011). Possibly, modality dominance during AV emotion processing might be more
variable in patients with the diagnosis of a psychotic disorder than the general population,
potentially contributing to the inconsistency of findings on aberrant emotional MSI in
previous studies (Lin et al., 2020; Tseng et al., 2015).
To sum up, prior evidence suggested altered MSI of emotional-laden information in
psychosis, although the results did not support clear conclusions regarding the direction of
impairments. Possibly, disturbances in emotional MSI in psychosis might not be generalizable
as being generally reduced or excessive. Further, they might as well largely depend on the
situation, i.e. the given task (Tseng et al., 2015).

25
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
The inconsistency of evidence regarding emotional MSI in psychosis does not lend
support for the assumption that psychosis is associated with deficient MSI in terms of
generally insufficient integration, assumed to be even more pronounced in social compared to
non-social stimuli (Tseng et al., 2015). However, the majority of prior studies suggested at
least dysfunctional aberrant emotional MSI in psychosis. Apart above mentioned factors,
which potentially influenced the inconsistent results, it might be speculated that impairments
of emotional MSI in psychosis might not manifest in a one-dimensional, generalized deficit
but rather a multi-faceted, dysfunctional alteration in processing crossmodal emotional
stimuli. In that perspective, dysfunctional emotional MSI in psychosis might express as
reduced integration under certain circumstances and excessive in other circumstances, with
potential maladaptive cognitive or behavioral consequences in either case.
1.4 A Potential Role of Dysfunctional Emotional MSI for Psychosis Development
While theoretical approaches regarding the influence of dysfunctional emotional MSI
on psychosis speculated that it might play a role in disorder development (Tseng et al., 2015),
previous studies of emotional MSI in psychosis mostly investigated samples of patients who
had already been diagnosed with a psychotic disorder. However, to our knowledge no study of
emotional MSI in a sample with psychosis proneness has been published.
Giannitelli et al. (2015) investigated emotional MSI in children with the diagnosis of
early-onset schizophrenia (EOS). Their findings of poorer uni-and crossmodal performance
compared to healthy controls mirror the deficit pattern in adult patients (Giannitelli et al.,
2015). This suggested that emotional MSI impairments might already be present in the early
developmental trajectory of psychosis1. However, caution in generalizing the findings of
Giannitelli et al. (2015) to the development trajectory of adult-onset psychosis might be
advised: EOS is a particularly rare form of schizophrenia (Driver et al., 2013) has been found
to show significant higher premorbid impairments and symptom load (e.g. Vyas et al., 2011).
This raises the question if the development trajectories concerning emotion processing deficits
are sufficiently similar between EOS and adult-onset psychosis.
Further, several studies on unimodal emotion processing indicated deficient
recognition of facial and vocal affect in psychosis proneness (van Donkersgoed et al., 2015).
1 Throughout this chapter, the term „psychosis“ refers to adult-onset psychosis. EOS will be referred to as such
to avoid confusion between both types of disorder manifestation.

26
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Since MSI reflects a non-linear gain mechanism beyond simple addition of unisensory
processes (Stein et al., 2010), it can be assumed that deficits in MSI might reflect specific
dysfunctions beyond summation of unisensory processing deficits.
In sum, previous studies of unisensory emotion processing in psychosis proneness as
well as prior findings of deficient emotional MSI in EOS offer hints towards potential
impairments of emotional MSI in psychosis proneness. However, to contribute to the
assumptions of deficient MSI of social cues constituting a risk factor in the development of
psychotic symptoms, studies with proneness samples or first-degree relatives are needed.
1.5 Research Question
Therefore, in this study we aimed to investigate MSI of emotional AV information in a
healthy sample with high psychosis proneness compared to a sample with low proneness.
Subjects categorized the emotional content of facial expressions as well as vocal prosody and
rated the respective perceived emotional intensity while one modality was attended and the
other ignored (paradigm adopted from Föcker et al., 2011).
In line with findings of altered processing of affective laden AV information in patient
samples as well as deficient unisensory facial or vocal emotion processing deficits in at-risk
samples, we expected the high proneness group to show aberrant emotion categorization
performance benefits and interference by crossmodal emotional in-/congruency compared to a
low proneness group, reflecting atypical emotional MSI. Further, we expected in-/congruency
effects during emotion categorization to be associated with self-reported psychotic
experiences such as everyday anomalous percepts, hallucinatory experiences and paranoid
ideation. Since the interpretation of perceptual anomalies is influenced by negative schemata
about the self and others (Garety et al., 2001), we also expected an association between
in/congruency effects during categorization performance and negative schemata.
2 Methods
2.1 Participants
We recruited healthy participants from the local community and amongst university
students. After initial contact, participants received a link leading to an online screening (see
2.3 General Procedure), which served to allocate subjects to either a high proneness group or

27
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
a low proneness group by means of a cut-off value (≥9) of the positive subscale score of the
Community Assessment of Psychic Experiences (CAPE; Stefanis et al., 2002).
Subjects with a present or past diagnosis of a mental disorder, especially of a psychotic
disorder, bipolar disorder or autism, as well as acute suicidality, neurological disorders,
regular and/or recent consumption of psychedelic substances, uncorrected sight or hearing
impairment or inability to follow task instructions were excluded. Since empirical evidence
indicated higher occurrence of substance abuse (Addington et al., 2014), anxiety (McAusland
et al., 2017) and depression (Verdoux et al., 1999) in samples with proneness to psychosis, we
did not exclude subjects with mild forms of substance abuse, anxiety disorders and depressive
disorders.
87 subjects fulfilled our criteria and were invited to the experimental session. We had to
exclude n = 3 in the high and n = 3 in the low proneness group due to technical difficulties
during data collection, n = 1 in the high and n = 5 in the low proneness group due to inability
to follow task instructions (see 2.4 Data Analysis), and n = 2 in the high proneness and n = 1
in the low proneness group since behavioural performance deviated more than two SD from
the respective group mean.
The final sample consisted of N = 72 participants, with n = 36 in the high proneness
group and n = 36 in the low proneness group. There were no associations between group and
both gender, Χ2(2) = 2.16, p = .339, φ = 0.17, and education level, Χ2(2) = 3.01, p = .222, φ =
0.21, and groups did not differ in age, t(70) = 0.87, p = .385, Cohen’s d = 0.21 (see Table 1 for
demographic data). Participants gave written informed consent prior to participation and
received 10€/hour or course credits as compensation. This study was approved by the Local
Ethics Committee of the University of Hamburg.
Table 1
Demographic and Diagnostic Data
High Proneness Low Proneness
n 36 36
Age, M (range) 24.8 (19-39) 25.9 (18-42)

28
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Gender, n (%)
female male
diverse
29 (80.6)
6 (16.7)
1 (2.8)
26 (72.2)
10 (27.8)
0
Education, n
10 years 12-13
years a university
degree b
1
27
8
2
20
14
CAPE positive, M (SD) 14.0 (6.2) 4.3 (2.1)
CAPS, M (SD) 11.3 (6.4) 5.7 (4.3)
LSHS-E, M (SD) 15.3 (9.7) 8.6 (7.1)
PCL, M (SD) c 47.3 (27.1) 34.8 (26.3)
BCSS n.S., M (SD) 4.2 (3.1) 3.3 (2.7)
BCSS n.O., M (SD) 4.8 (3.3) 3.8 (3.9)
Notes. N = 72. CAPE positive = Community Assessment of Psychic Experiences, positive subscale; CAPS =
Cardiff Anomalous Perception Scale, total score; LSHS-E = Launey-Slade Hallucination Scale-Extended, total
score; PCL= Paranoia Checklist, total score; BCSS n.S. = Brief Core Schema Scales, negative self subscale;
BCSS n.O. = Brief Core Schema Scales, negative other subscale.
a due to changes in German education law in 2007, the years of education for acquire the Abitur (A-level/high
school equivalent) vary between 12-13 years depending on school and Bundesland; b university degree: Bachelor
level or higher. c one subject in the low and one in the high proneness group had ≥50% missings in the PCL.
Their PCL scores were corrected by the respective group mean.
2.2 Stimuli and Experimental Paradigm
Experimental procedure was adopted from Föcker et. (2011), using the Software
Presentation® (Version 21.1; Neurobehavioural Systems Inc., Berkeley, California, USA). In
total, 216 emotionally laden AV stimuli were presented centrally on a computer screen (61cm
diameter, screen resolution: 1920 x 1200) at 65cm viewing distance (4° width and 9° height of
visual angle) and via computer screen loudspeakers (60 to 65 dB, measured at participants’
head position). Stimuli consisted of visual and acoustic recordings of 4 actors (2 female, 2

29
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
male) uttering bisyllabic German pseudowords (“lolo”, “tete”, “gigi”). Visual stimuli
consisted of video recordings of the actor’s inner facial features during pseudoword utterance,
acoustic stimuli of the auditory stream of the pseudoword utterance (for stimulus creation and
selection, see Föcker et al., 2011). Face expressions and prosody contained one of 4 emotions:
happy, angry, sad or neutral. Stimuli were either unimodal visual (mean duration 761ms, range
500-1400), unimodal acoustic (mean duration 761ms, range 500-1400), bimodal emotionally
congruent (mean duration 946ms, range 734-1468) or bimodal emotionally incongruent (mean
duration 904ms, range 633-1501), with 48 stimuli per stimulus condition. For both bimodal
conditions, the auditory stream and the video originated from different recordings.
Additionally, visual and acoustic deviant stimuli (6 per stimulus condition) were presented to
check whether participants paid attention to the task over the course of the experiment. Visual
deviants included a black dot (0,6°/ 6mm diameter, duration 100ms) in one of 4 possible
locations (forehead, nose, left or right cheek) during last 130-330ms of the video, acoustic
deviants one of four tones (600/900/1200 or 1500Hz, duration 100ms) during the last 130-
330ms of the auditory stream.
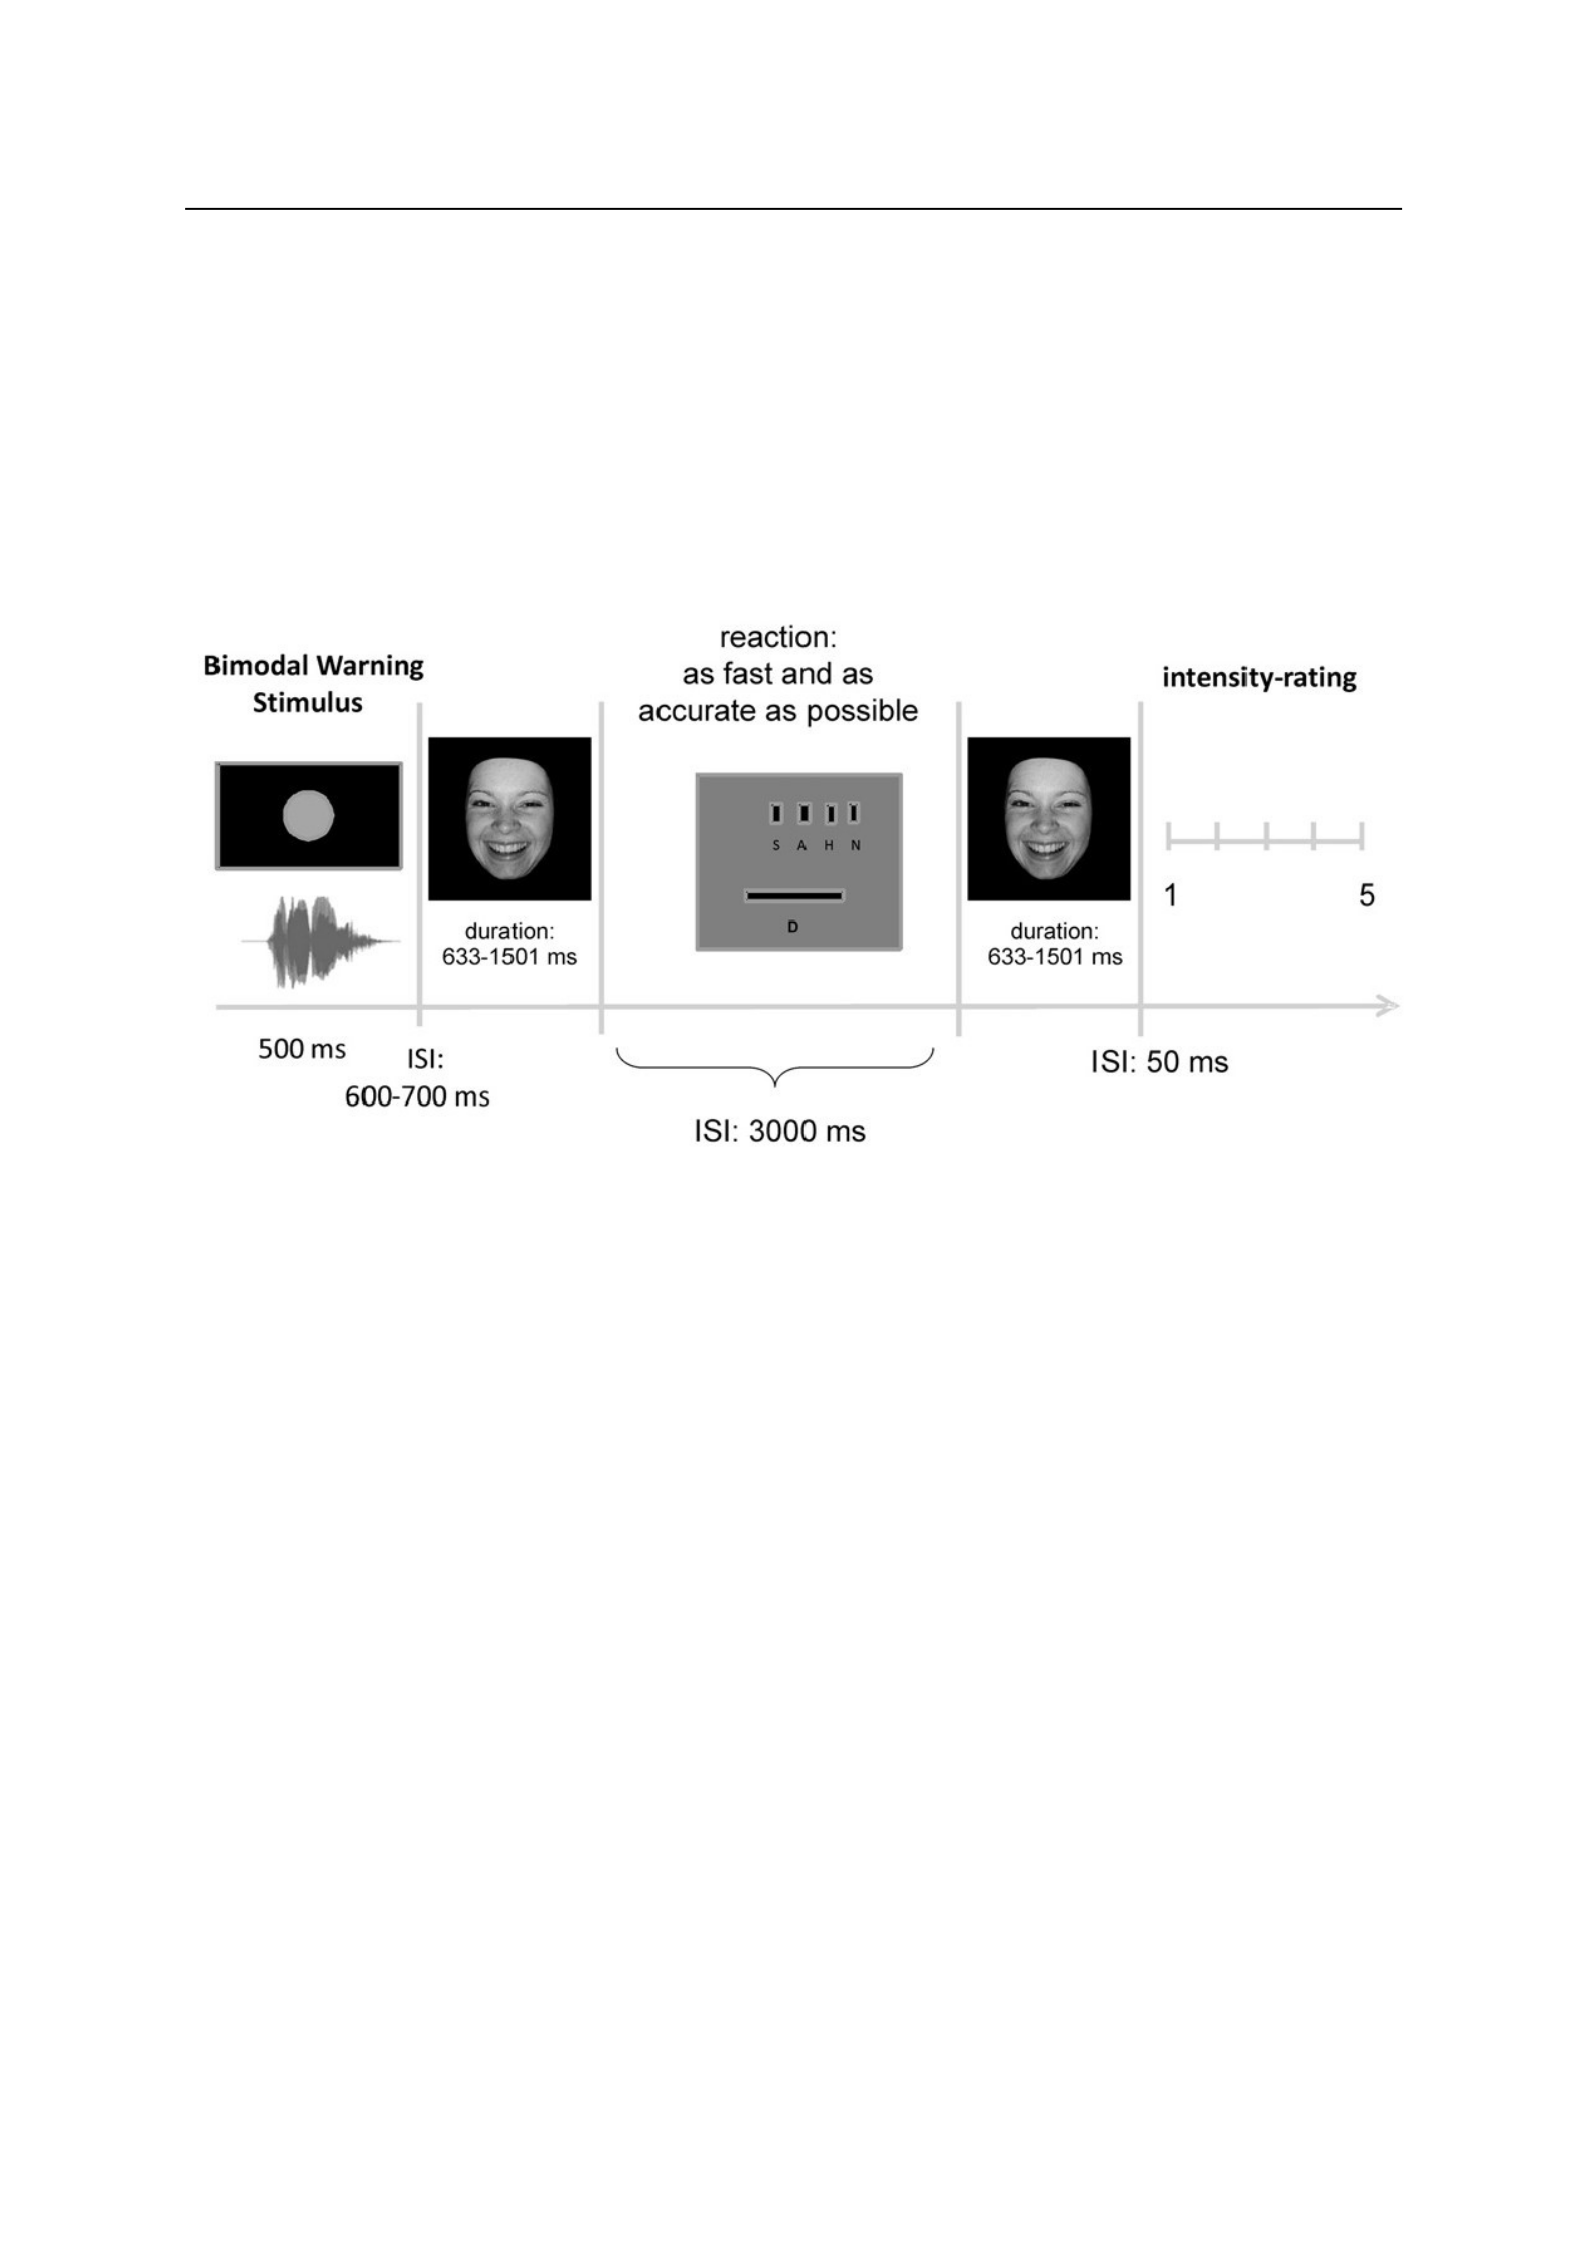
After a bimodal warning stimulus (grey circle with 2° of visual angle combined with
multispeaker noise, duration = 500ms), each stimulus was presented twice in a row after a
random Inter-Stimulus-Interval (600-700ms, uniform distribution), Following the first onset,
subjects were asked to categorize the perceived emotion as fast and accurately as possible by
button press on a custom German keyboard. Each of the four buttons was designated to one of
the four emotions as well as to one of four fingers of the right hand (index to little finger). The
assignment order of emotion category to the buttons was balanced across participants. After
an Inter-Stimulus-Interval of 3000ms, the same stimulus was presented a second time. After
offset, a rating scale appeared on the screen and participants had to rate the intensity of the
perceived emotion from 1 (very low) to 5 (very high) by pressing the respective key (1-5) on
the keyboard. Immediately after intensity rating, the next trial started. In case of deviants,
participants had to press the space bar following the first presentation to indicate that they
recognized the deviant. After pressing the space bar, the next trial started immediately (see
Figure 2 for a depiction of the trial structure).
Stimuli were presented randomly in 12 blocks of 27 stimuli each. For half of the blocks,
participants were asked to attend to the face and ignore the voice and vice versa. Unimodal
30
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
stimuli were only used in blocks in which the corresponding modality had to be attended. The
order of blocks was randomized across participants. Half of the participants started with
attend face, the other half with attend voice. After each block, participants could take a short
break of 2-3 minutes.
Figure 2
Experimental Design
Note. ISI = Inter-Stimulus-Interval. Capital letters represent buttons for emotion categorization: S = sad, A =
angry, H = Happy, N = Neutral, D = deviant recognition via space bar. Adopted from “Preattentive processing of
audio-visual emotional signals” by J. Föcker, M. Gondan, & B. Röder, 2011, Acta Psychologica, 137(1), 36-47
(https://doi.org/ 10.1016/j.actpsy.2011.02.004).
2.3 General Procedure
Prior to the experimental session, subjects completed an online screening. In the
screening, demographic data was collected and in- and exclusion criteria were checked. The
main aim of the screening was administering the 28-item version of the CAPE (Stefanis et al.,
2002), a self-report questionnaire measuring life-time occurrence of psychotic symptoms, as a
measure for proneness to psychosis. We applied a cut-off value of (≥9) of the positive
subscale to assign subjects to one of two subgroups (high proneness ≥9 & low proneness <9).
This value has been used previously to distinguish subjects with low and high proneness to
psychosis (Krkovic et al., 2020).
The experimental session took place in a sound attenuated and dimly lit room at the
University of Hamburg. Prior to the experimental run, baseline diagnostic measures were
conducted. These included personal and familiar history of psychotic disorders, regular

31
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
medication intake, recent substance consumption, sight or hearing impairment and respective
corrections, handedness, the Trail Making Test (TMT) Version A and Version B (Reitan &
Wolfson, 1985) for measuring attention and processing speed and the Continuous
Performance Test – Identical Pairs (CPT-IP; Nuechterlein et al., 2008) for measuring
vigilance.
Subsequently, participants completed the experimental paradigm (adopted from Föcker
et al., 2011) as described above. 10 practice trials were conducted prior to the actual
experimental run to familiarize participants with the task. The experimental run took
approximately 50 min to complete.
After the experimental run, participants completed the following self-report instruments:
The Launey-Slade Hallucination Scale-Extended (LSHS-E; Siddi et al., 2019;
Lincoln et al., 2009) for measuring hallucinatory experiences, the Paranoia Check-List (PCL;
Freeman et al., 2005) for measuring paranoid thoughts and convictions, the Cardiff
Anomalous Perception Scale (CAPS; Bell et al., 2006) for measuring anomalous perceptual
experiences and the Brief Core Schema Scales (BCSS; Fowler et al., 2006) for measuring
positive and negative schemata about the self and others (a glossary of the instruments and
questionnaires used in this dissertation project can be found in Table A.1 in Appendix A).
2.4 Data Analysis
To examine group differences in age or in distributions of gender and education level,
we calculated an unpaired t-test for age and Χ2-tests for gender and education level.
For each subject, experimental data was preprocessed using RStudio Version 1.0.143
(RStudio Team, 2016) by calculating mean RT (in ms) and accuracy (proportion of correct
emotion categorizations, in %) for categorization data as well as mean perceived emotional
intensity, separately per stimulus condition (unimodal, bimodal congruent and bimodal
incongruent) and attention condition (attend face vs. attend voice). Incorrectly categorized
stimuli or responses latencies below 200ms and above 3950ms were excluded from analysis.
Deviant trials were analyzed separately (see paragraph below). To account for a possible
speed-accuracy trade-off, we calculated inverse efficiency (IE) scores for categorization data
by dividing mean RT by accuracy (Townsend & Ashby, 1978). Statistical analyses were
performed using IBM SPSS Statistics for Windows, Version 27.0 (IBM Corp., 2020).

32
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
To examine whether participants followed task instructions, we calculated the
percentage of total recognized deviants for each participant. If less than 60 percent were
recognized, the participant was excluded from analysis. Further, we calculated an unpaired
ttest to check for group differences in deviant recognition.
IE scores were analyzed for group differences by means of mixed ANOVAs with the
between-factor Group (high vs. low proneness) and the within-factor Stimulus Condition
(unimodal vs. bimodal emotionally congruent vs. bimodal emotionally incongruent). Since we
were not primarily interested in effects of attention condition for our hypotheses, we ran one
mixed ANOVA each for both attention conditions. We applied the Huynh-Feldt correction
(Huynh & Feldt, 1976) in case of sphericity violations. Post-hoc pairwise comparisons were
calculated by means of Bonferroni corrected t-test. The same analyses were run for mean
perceived intensity and, following the analysis strategy of Föcker et al. (2011) additionally for
mean RT and accuracy (see Appendix B).
Further, we explored if both groups differed in emotion recognition performance
regarding the target emotion. Therefore, we additionally calculated mean RT, accuracy and
mean perceived intensity separately for each of the four target emotions per participant. IE
scores could not be calculated due to low accuracy scores in some target emotion * stimulus
condition * attention condition combinations. We observed that calculating IE scores would
result in very high extreme values and violations of analysis requirements. Mean RT, accuracy
and mean perceived intensity were exploratory analyzed by means of mixed ANOVAs with
the factors Group and Stimulus Condition, separately for each target emotion and attention
condition, followed by Bonferroni-corrected post-hoc t-tests (for an overview over inferential
statistics of all emotion-specific mixed ANOVAs, F-statistic, p-values and η2p for each mixed
ANOVA are additionally reported in Table B.2 in Appendix B). Post-hoc comparisons for the
within-factor Stimulus Condition are reported between congruent and unimodal trials,
regarding a possible congruency facilitation effect (lower RT, higher accuracy, and higher
perceived emotional intensity in congruent compared to unimodal trials), and between
incongruent and unimodal trials, regarding a possible incongruency interference effect (higher
RT, lower accuracy, and lower perceived emotional intensity in incongruent compared to
unimodal trials). Comparisons between congruent and incongruent trials are not informative
for the research question and are hence not reported for readability reasons.

33
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Potential group differences in attention and processing speed were analyzed by means
of unpaired t-Tests entering TMT-A and -B completion times. To check for group differences
in vigilance, CPT-IP d’ scores, a sensitivity score reflecting attentional capacity (Cornblatt et
al., 1988), were analyzed with a mixed ANOVA with the between factor Group (high vs. low
proneness) and the within-factor Digit Load (2 vs. 3 vs. 4 digits), followed by post-hoc t-tests.
In case of significant group differences in the TMT or CPT-IP, we assessed the influence of
the control variable on the main dependent variable (IE) by means of Pearson’s correlation
coefficients r.
CAPS, LSHS-E, PCL, BCSS negative self and BCSS negative other scores were
compared between high and low proneness groups by means of unpaired t-tests, separately for
each questionnaire.
To examine associations between in-/congruency effects and psychotic experiences as
well as negative schemata, we first calculated IE-difference scores between the IE scores of
each stimulus condition pairing (congruent - unimodal, unimodal - incongruent, congruent -
incongruent), separately for both attention conditions. We then calculated Bonferronicorrected
Pearson correlation coefficients (r) between IE-difference scores and CAPS, LSHSE, PCL as
well as BCSS negative subscale scores.
Additionally, we calculated Bonferroni-corrected Pearson’s correlation coefficients (r)
between IE scores and CAPS, LSHS-E, PCL, as well as BCSS negative subscale scores to
explore associations between emotional categorization performance and psychotic
experiences as well as negative schemata. For all correlations, Pearson’s correlation
coefficients r > .3 were highlighted as potentially meaningful for further discussion.
3 Results
3.1 Experimental Data
3.1.1 Deviant Recognition
Groups did not differ in percentage of recognized deviants (high proneness: M = 88.65,
SD = 10.23; low proneness: M = 84.61, SD = 10.33), t(70) = -1.67, p = .099, Cohen’s d = 0.39.

34
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
3.1.2 Inverse Efficiency Analysis
Attend Face. A 2 (Group) x 3 (Stimulus Condition) mixed ANOVA for IE scores in
attend face blocks revealed a significant main effect of Stimulus Condition, F(1.6, 112.07) =
35.94, p < .001, η2p = 0.34, indicating lower IE-scores in the congruent condition (M =
1780.67, SD = 348.64) compared to both the unimodal (M = 1898.02, SD = 395.64), t(71) = -
4.70, p < .001, and the incongruent condition (M = 2082.07, SD = 454.11), t(71) = -7.13, p
< .001, as well as lower IE scores in the unimodal condition compared to the incongruent
condition, t(71) = -4.92, p < .001. There was no main effect of Group, F(1, 70) = 1.88, p
= .175, η2p = 0.03, or Group * Stimulus Condition interaction, F(1.6, 112.07) = 0.23, p = .748,
η2p = 0.003 (see Figure 3 top row for IE scores per group and stimulus condition).
Attend Voice. A 2 (Group) x 3 (Stimulus Condition) mixed ANOVA for IE scores in
attend voice blocks revealed a significant main effect of Stimulus Condition, F(1.26, 88.05) =
120.59, p < .001, η2p = 0.63, indicating lower IE-scores in the congruent condition (M =
1800.01, SD = 357.85) compared to both the unimodal (M = 1983.38, SD = 327.15), t(71) =
8.64, p < .001, and the incongruent condition (M = 2466.80, SD = 544.06), t(71) = -12.19, p
< .001, as well as lower IE scores in the unimodal condition compared to the incongruent
condition, t(71) = -9.84, p < .001. There was no main effect of Group, F(1, 70) = 0.002, p
= .964, η2p < 0.001, and no Group * Stimulus Condition interaction, F(1.26, 88.05) = 0.43, p =
.559, η2p = 0.006 (see Figure 3 top row for IE scores per group and stimulus condition).
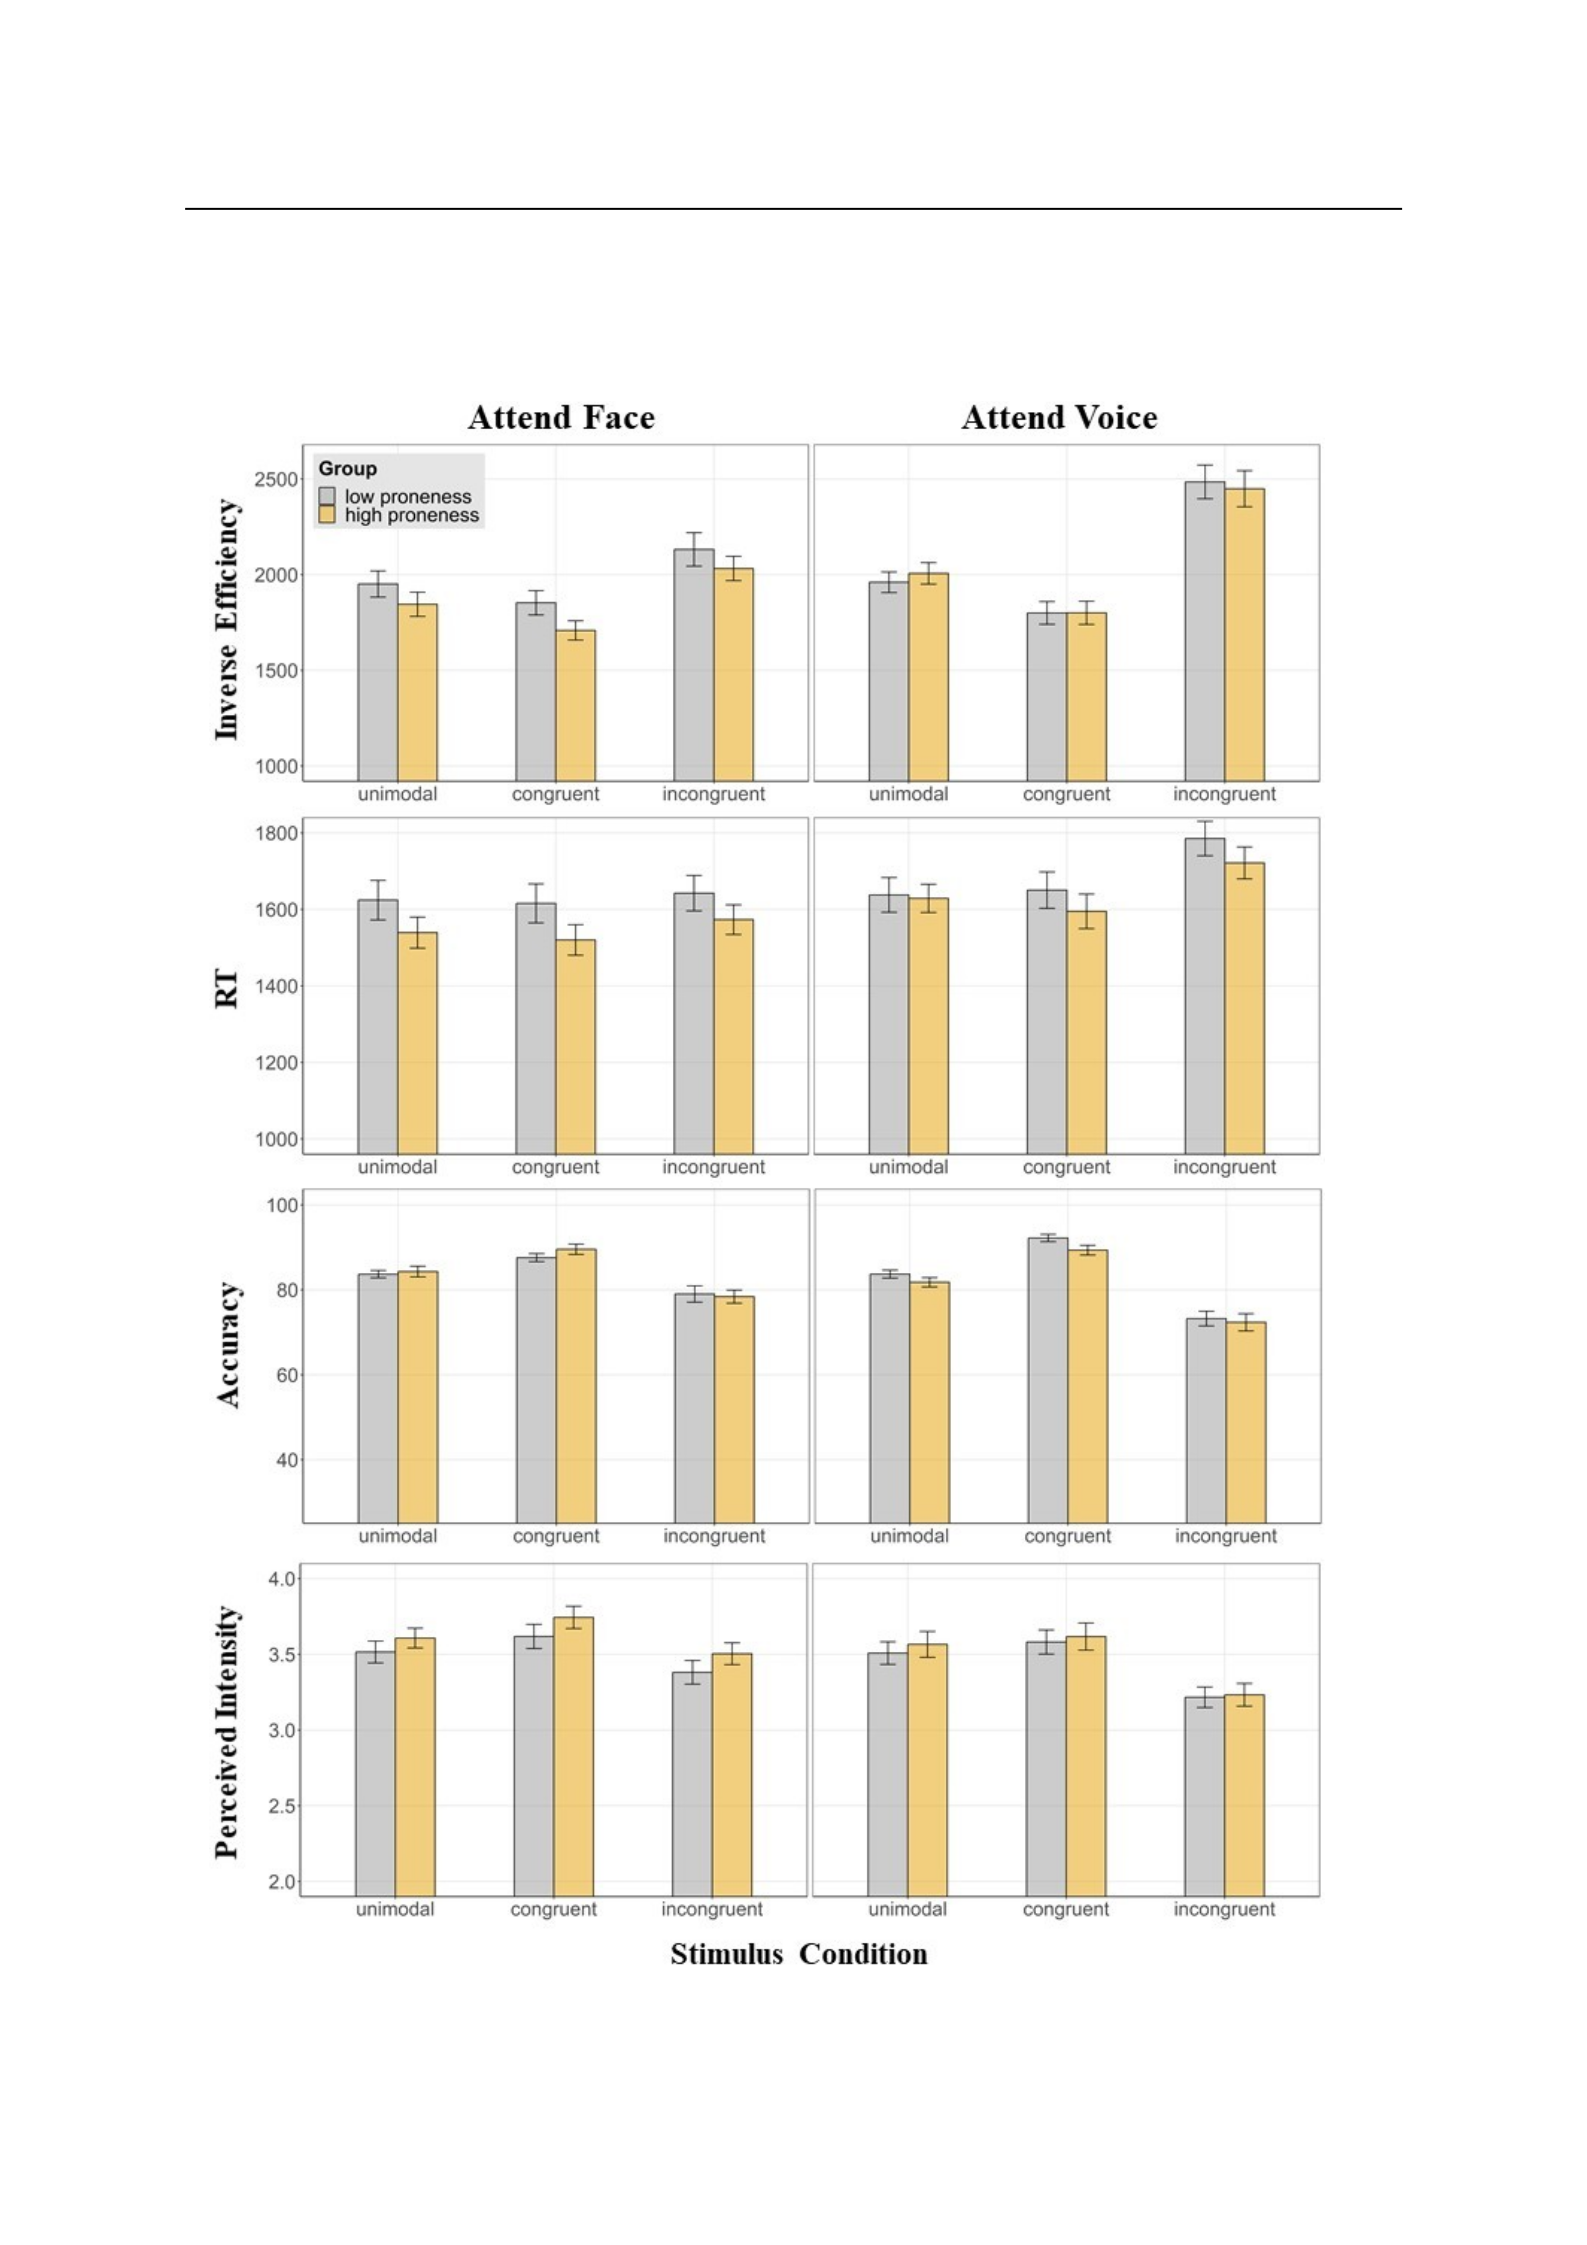
35
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Figure 3
Inverse Efficiency Scores, mean RT, Accuracy and mean Perceived Emotional Intensity per
Group and Stimulus Condition, Separated by Attention Condition
Notes. nlow = 36, nhigh = 36. Error bars denote ±1 standard error of the mean. congruent = bimodal emotionally
congruent; incongruent = bimodal emotionally incongruent.

36
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Exploratory Analysis with Attention as Within-Factor. To check for potential
attention-specific group differences, we calculated an exploratory mixed ANOVA with the
between-factor Group (high vs. low proneness) and the within-factors Stimulus Condition
(unimodal vs. bimodal emotionally congruent vs. bimodal emotionally incongruent) and
Attention (attend face vs. attend voice). There were significant main effects of the
withinfactors Stimulus Condition, F(1.34, 93.6) = 121. 2, p < .001, η2p = 0.63, and Attention,
F(1, 70) = 38.5, p < .001, η2p = 0.36, indicating overall lower IE-scores in attend face blocks
(M = 1920.26.7, SD = 363.11) compared to attend voice blocks (M = 2083.40, SD = 360.80).
Stimulus Condition and Attention significantly interacted with each other, F(1.45, 101.33) =
30.92, p < .001, η2p = 0.31. Post-hoc t-tests for the Stimulus Condition * Attention interaction
revealed lower IE scores in the attend face compared to the attend voice condition in
incongruent trials (face: M = 2082.07, SD = 457.12; voice: M = 2466.80, SD = 544.06) t(71)
= -6.91, p < .001, and in unimodal trials (face: M = 1898.02, SD = 395.64; voice: M =
1983.39, SD = 327.15), t(71) = -3.18, p = .002, but not in congruent trials (face: M = 1780.68,
SD = 348.64; voice: M = 1800.01, SD = 357.85), t(71) = -0.68, p = .499. Further, there was a
significant interaction between Group * Attention, F(1, 70) = 5.26, p = .025, η2p = 0.07.
Posthoc t-tests for the Group * Attention interaction revealed that the high proneness group
showed significantly lower IE scores in attend face trials (M = 1861.91, SD = 323.51)
compared to attend voice trials (M = 2085.36, SD = 375.34), t(35) = -6.55, p < .001, Cohen’s
d = -1.09. For the low proneness group, the difference in IE scores between attend face (M =
1978.60, SD = 394.73) and attend voice trials (M = 2081.44, SD = 350.97) was also
significant, t(35) = -2.57, p = .015, Cohen’s d = -.043, but smaller compared to the high
proneness group. There was no main effect of Group, F(1, 70) = 0.48, p = .49, η2p = 0.007, no
Group * Stimulus Condition interaction, F(1.34, 93.6) = 0.26, p = .677, η2p = 0.004, and no
Group * Stimulus Condition * Attention interaction, F(1.45, 101.33) = 0.49, p = .554, η2p =
0.007.
Correlation Between IE Difference Scores. Pearson correlation coefficients
calculated over all subjects revealed highly significant positive correlations between the IE
difference score congruent – incongruent and both the IE difference scores congruent –
unimodal and unimodal – incongruent, respectively, for both the attend face and attend voice
trials, all r > .4, all Bonferroni-corrected p < .001. There was no other significant correlation

37
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
between IE difference scores, all p > .05 (see Table 2 for Pearson’s r for correlations between
IE difference scores).
Correlations Between IE Scores. Pearson correlation coefficients over all subjects
showed that IE scores for all stimulus conditions and both attention conditions revealed highly
significant, strong correlations, all r ≥ .48 and Bonferroni-corrected p < .001 (see Table B.1 in
Appendix B for Pearson’s r for correlations between IE scores).
Table 2
Pearson Correlation Coefficients r Between IE Difference Scores and Questionnaire Data
1. 2. 3. 4. 5. 6. 7. 8. 9. 10.
1. IE: C-U
2. IE: U-I
3. IE: C-I
-.13
.48***
.81***
4. IE: C-U
5. IE: U-I
6. IE: C-I
.21
.19
.25
.11
.17
.20
.22
.27
.32
.06
.44***
.92***
7. CAPS -.24 -.03 -.17 -.15 -.03 -.08
8. LSHS-E -.19 .01 -.1 -.18 -.4 -.1 .7***
9. PCL a -.21 .08 -.05 .01 -.2 -.18 .42*** .52***
10.BCSS nS -.12 .15 .06 .04 .02 .03 .14 .27 .63***
11.BCSS nO .02 -.03 -.02 -.18 -.18 -.23 .28 .40* .52*** .29
Notes. N = 72. Pearson correlation coefficients r > .3 are marked in bold. p-values are Bonferroni-corrected. IE =
Inverse Efficiency; C-U = Difference in IE scores between congruent and unimodal conditions; U-I = Difference
in IE scores between unimodal and incongruent conditions; C-I = Difference in IE scores between congruent and
incongruent conditions; LSHS-E = Launey-Slade Hallucination Scale-Extended; PCL total = Paranoia Checklist,
total score; CAPS total = Cardiff Anomalous Perception Scale, total score; BCSS nS = Brief Core Schema
Scales, negative self subscale; BCSS nO = Brief Core Schema Scales, negative other subscale. a One subject in
the low and one in the high proneness group had ≥50% missings in the PCL. Their PCL scores were corrected by
the respective group mean.
* p < .05, ** p < .01, *** p < .001
Attend Face Attend Voice

38
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
3.1.3 Intensity Analysis
Attend Face. A 2 (Group) x 3 (Stimulus Condition) mixed ANOVA for mean
perceived emotional intensity in attend face blocks revealed a significant main effect of
Stimulus Condition, F(1.86, 130.44) = 28.42, p < .001, η2p = 0.29, indicating higher intensity
ratings in the congruent condition (M = 3.68, SD = 0.46) compared to both the unimodal (M =
3.56, SD = 0.41), t(71) = 4.56, p < .001, and the incongruent condition (M = 3.44, SD = 0.45),
t(71) = 6.71, p < .001, as well as higher intensity ratings in the unimodal condition compared
to the incongruent condition, t(71) = 3.73, p = .001. There was no main effect of Group, F(1,
70) =1.36, p = .248, η2p = 0.02 , and no Group * Stimulus Condition interaction, F(1.86,
130.44) = 0.17, p = .827, η2p = 0.002 (see Figure 3 bottom row for mean perceived emotional
intensity per group and stimulus condition).
Attend Voice. A 2 (Group) x 3 (Stimulus Condition) mixed ANOVA for mean
perceived emotional intensity in attend voice blocks revealed a significant main effect of
Stimulus Condition, F(1.88, 131.39) = 86.22, p < .001, η2p = 0.55, indicating higher intensity
ratings in the congruent condition (M = 3.60, SD = 0.51) compared to both the unimodal (M =
3.54, SD = 0.48), t(71) = 2.41, p = .019, and the incongruent condition (M = 3.22, SD = 0.43),
t(71) = 10.87, p < .001, as well as higher intensity ratings in the unimodal compared to the
incongruent condition, t(71) = 10.28, p < .001. There was no main effect of Group, F(1, 70) =
0.12, p = .731, η2p = 0.002 , and no Group * Stimulus Condition interaction, F(1.88, 131.39) =
0.23, p = .783, η2p = 0.003 (see Figure 3 bottom row for mean perceived emotional intensity
per group and stimulus condition).
Exploratory Analysis with Attention as Within-Factor. Analogue to the IE analysis,
we calculated an exploratory 2 (Group) * 3 (Stimulus Condition) * 2 (Attention) mixed
ANOVA for mean perceived emotional intensity. There were significant main effects of the
within-factors Stimulus Condition, F(1.68, 117.48) = 90.18, p < .001, η2p = 0.56, and
Attention, F(1, 70) = 20.47, p < .001 , η2p = 0.23, revealing overall higher intensity ratings in
attend face blocks (M = 3.56, SD = 0.41) compared to attend voice blocks (M = 3.45, SD =
0.45). The factors Stimulus Condition and Attention interacted significantly with each other,
F(2, 140) = 11.88, p < .001 , η2p = 0.15. Post-hoc t-tests for the Stimulus Condition * Attention
interaction revealed higher intensity ratings in the attend face compared to the attend voice
condition in congruent (face: M = 3.68, SD = 0.46; voice: M = 3.60, SD = 0.51), t(71) = 2.6, p

39
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
= .011, and incongruent trials (face: M = 3.44, SD = 0.45; voice: M = 3.22, SD = 0.43), t(71) =
6.16, p < .001, but not in unimodal trials (face: M = 3.56, SD = 0.41; voice: M = 3.53, SD =
0.48), t(71) = 0.72, p = .475. There was no main effect of Group, F(1, 70) = 0.57, p = .451, η2p
= 0.008, no Group * Stimulus Condition, F(1.68, 117.48) = 0.03, p = .953, η2p = < 0.001, no
Group * Attention, F(1, 70) = 2.57, p = .113, η2p = 0.04, and no Group * Stimulus Condition *
Attention interaction, F(2, 140) = 0.42, p = .657, η2p = 0.006.
3.1.4 Reaction Time and Accuracy
The supplementary analyses of mean RT and accuracy revealed no main effects and
interactions of the between-factor Group on neither mean RT nor accuracy. Further,
withineffects of the factor Stimulus Condition comparable to the effects published by Föcker
et al. (2011) could be observed on both mean RT and accuracy (see Appendix B for details on
the supplementary analyses of mean RT and accuracy).
3.1.5 Exploratory Emotion-Specific Analysis2
Target Emotion Happy. Separate Group * Stimulus Condition mixed ANOVAs in
attend face trials with target emotion happy revealed neither a main effect of Group, F(1, 70)
= 0.93, p = .338, η2p = 0.01, nor a main effect of Stimulus Condition, F(2, 140) = 1.79, p
= .171, η2p = 0.03, on mean RT. There was a non-significant trend for a Group * Stimulus
Condition interaction on mean RT in attend face trials, F(2, 140) = 2.97, p = .055, η2p = 0.04.
Post-hoc comparisons revealed a non-significant trend for lower mean RT in the high
proneness compared to the low proneness group in congruent happy face trials, t(70) = -1.83,
p = .072, Cohen’s d = -0.43, but not in unimodal, t(70) = -0.67, p = .505, Cohen’s d = -0.16, or
incongruent trials, t(70) = -0.29, p = .775, Cohen’s d = -0.07. The high proneness group
showed a congruency facilitation effect, t(35) = -2.22, p = .033, Cohen’s d = -0.37, but no
incongruency interference effect t(35) = 1.11, p = .275, Cohen’s d = 0.19, on mean RT in
happy face stimuli, whereas the low proneness group neither showed a congruency
facilitation, t(35) = 0.41, p = .688, Cohen’s d = 0.07, nor an incongruency interference effect,
t(35) = 0.12, p = .907, Cohen’s d = 0.02. There was neither a main effect of Group, F(1, 70) =
2.06, p = .156, η2p = 0.03, nor a Group * Stimulus Condition interaction, F(1.74, 121.74) =
0.99, p = .366, η2p = 0.01, on accuracy in attend face trials. The factor Stimulus Condition
showed a non-significant trend for a main effect on accuracy in attend face trials, F(1.74,
2 For an overview over inferential statistics of all emotion-specific mixed ANOVAs, F-statistic, p-value and η2p
for each mixed ANOVA are additionally reported in Table B.2 in Appendix B.

40
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
121.74) = 2.75, p = .075, η2p = 0.04, revealing a congruency facilitation effect on accuracy in
happy face stimuli, t(71) = 2.72, p = .022, Cohen’s d = 0.32 . Further, there was no main effect
of Group, F(1, 70) = 1.04, p = .312, η2p = 0.02, and no Group * Stimulus Condition interaction
on mean perceived intensity in attend face trials, F(2, 140) = 0.6, p = .549, η2p = 0.009. There
was a significant main effect of Stimulus Condition on mean perceived intensity in attend face
trials, F(2, 140) = 5.46, p = .005, η2p = 0.07, indicating a non-significant trend for a
congruency facilitation effect when rating happy face stimuli, t(71) = 2.30, p = .073, Cohen’s
d = 0.27.
Separate Group * Stimulus Condition mixed ANOVAs in attend voice trials with target
emotion happy revealed no main effect of Group on mean RT, F(1, 68) = 0.51, p =
.479, η2p = 0.007. There was a highly significant main effect of Stimulus Condition, F(2, 136)
= 42.31, p < .001, η2p = 0.38, and a non-significant trend for a Group * Stimulus Condition
interaction, F(2, 136) = 3, p = .053, η2p = 0.04, on mean RT in attend voice trials. Post-hoc
comparisons revealed similar mean RT for both groups in unimodal, t(70) = -0.1, p = .919,
Cohen’s d = -0.02, congruent, t(70) = -0.75, p = .454, Cohen’s d = -0.18, and incongruent
happy voice trials, t(68) = .1,61, p = .113, Cohen’s d = -0.38. The high proneness group
showed both a congruency facilitation, t(35) = -2.29, p = .029, Cohen’s d = -0.38, and an
incongruency interference effect, t(34) = 2.63, p = .013, Cohen’s d = 0.44, on mean RT in
happy voice trials, whereas the low proneness group showed an incongruency interference,
t(34) = 6.37, p < .001, Cohen’s d = 1.08, but no congruency facilitation effect, t(35) = -0.92, p
= .363, Cohen’s d = -0.15. There was no main effect of Group on accuracy in attend voice
trials, F(1, 70) = 0.21, p = .645, η2p = 0.003. There was a highly significant main effect of
Stimulus Condition, F(1.63, 114.25) = 153.04, p < .001, η2p = 0.69, and a non-significant trend
for a Group * Stimulus Condition interaction, F(1.63, 114.25) = 2.54, p = .094, η2p = 0.04, on
accuracy in attend voice trials. Post-hoc comparisons revealed similar accuracy for both
groups in unimodal, t(70) = -1.0, p = .321, Cohen’s d = -0.24, congruent, t(70) = 0.74, p
= .465, Cohen’s d = 0.17, and incongruent happy voice trials, t(70) = 1.13, p = .264, Cohen’s
d = 0.27. The high proneness group showed both a congruency facilitation, t(35) = 7.61, p
< .001, Cohen’s d = 1.27, and incongruency interference effect, t(35) = -5.49, p < .001,
Cohen’s d = 0.92, on accuracy in happy voice trials. Both a congruency facilitation, t(35) =
4.85, p <

41
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
.001, Cohen’s d = 0.81, and an incongruency interference effect, t(35) =-9.57, p < .001,
Cohen’s d = -1.59, on accuracy in happy voice trials could also be observed in the low
proneness group. There was no main effect of Group, F(1, 70) = 0.15, p = .703, η2p = 0.002,
and no Group * Stimulus Condition interaction, F(2, 140) = 0.2, p = .819, η2p = 0.003, on
mean perceived intensity in attend voice trials. The main effect of Stimulus Condition on
mean perceived intensity in attend voice trials was highly significant, F(2, 140) = 54.95, p
< .001, η2p = 0.44, revealing both a congruency facilitation effect, t(71) = 5.54, p < .001,
Cohen’s d = 0.65, and an incongruency interference effect, t(71) = -5.62, p < .001, Cohen’s d
= -.066, when rating happy face stimuli.
In sum, both groups overall showed similar mean RT, accuracy and mean intensity
ratings in both attend face and voice trials with target emotion happy. Overall, congruency
facilitation and/or incongruency interference effects could be found for all measures in trials
with target emotion happy in both attention conditions except for mean RT in attend face
trials. In attend face trials, the high proneness group showed both a congruency facilitation
and an incongruency interference effect on mean RT, whereas the low proneness group
showed neither effect. Apart from this, both groups showed a comparable pattern of
in/congruency effects for all measures in happy face and voice trials (see Figure 4 top row for
mean RT, accuracy and mean perceived intensity for target emotion happy).
Target Emotion Angry. Separate Group * Stimulus Condition mixed ANOVAs in
attend face trials with target emotion angry revealed neither a main effect of Group, F(1, 70) =
1.7, p = .196, η2p = 0.02, nor of Stimulus Condition, F(2, 140) = 2.30, p = .104, η2p = 0.03, and
no Group * Stimulus Condition interaction, F(2, 140) = 0.77, p = .464, η2p = 0.01, on mean
RT. There was no main effect of Group on accuracy in attend face trials, F(1, 70) =
1.26, p = .265, η2p = 0.02, and no Group * Stimulus Condition interaction, F(1.58, 110.73) =
0.95, p = .372, η2p = 0.01 (note: there was no homogeneity of covariances in accuracy in angry
face trials, Box-test p = .001, prohibiting an interpretation of the interaction). The main effect
of Stimulus Condition on accuracy in attend face trials was highly significant, F(1.58, 110.73)
= 14.52, p < .001, η2p = 0.17, indicating an incongruency interference effect on accuracy in
angry face stimuli, t(71) = -4, p < .001, Cohen’s d = -0.47. There was no main effect of
Group, F(1, 70) = 0.64, p = .425, η2p = 0.009, and no Group * Stimulus Condition interaction,
F(1.53, 107.28) = 0.002, p = .994, η2p < 0.001, on mean perceived intensity in attend face

42
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
trials. The main effect of Stimulus Condition on mean perceived intensity in attend face trials
was highly significant, F(1.53, 107.28) = 14.47, p < .001, η2p = 0.17, indicating an
incongruency interference effect on intensity ratings in angry face stimuli, t(71) = -3.30, p
= .005, Cohen’s d = -0.39.
Separate Group * Stimulus Condition mixed ANOVAs in attend voice trials with target
emotion angry revealed no main effect of Group on mean RT, F(1, 70) = 0.09, p = .769, η2p =
0.001. There was a highly significant main effect of Stimulus Condition, F(2, 140) = 20.76, p
< .001, η2p = 0.23, and a significant Group * Stimulus Condition interaction, F(2, 140) = 3.24,
p = .042, η2p = 0.04, on mean RT in attend voice trials. Post-hoc comparisons revealed similar
mean RT for both groups in unimodal, t(70) = 0.70, p = .487, Cohen’s d = 0.17, congruent,
t(70) = -0.6, p = .549, Cohen’s d = -0.14, and incongruent angry voice trials, t(70) = 0.78, p
= .438, Cohen’s d = 0.18. The high proneness group showed an incongruency interference,
t(35) = 4.21, p < .001, Cohen’s d = 0.7, but no congruency facilitation effect, t(35) = -1.02, p
= .314, Cohen’s d = -0.17, on mean RT in angry voice trials, whereas the low proneness group
showed an incongruency interference effect, t(35) = 4.47, p < .001, Cohen’s d = 0.74, and a
non-significant trend for higher mean RT in congruent compared to unimodal angry voice
trials, t(35) = 2.03, p = .051, Cohen’s d = 0.34. A mixed ANOVA on accuracy in attend voice
trials could not be interpreted due to violations of homogeneity of error variances (Levene-test
p < .05). Following a recommendation by Hsu (1996), post-hoc comparisons are reported.
Post-hoc comparisons revealed lower accuracy in the high proneness (M = 78.88, SD = 10.72)
compared to the low proneness group (M = 84.51, SD = 6.93) during categorization of angry
voice stimuli, t(59.89) = -2.64, p = .010, Cohen’s d = -0.62. A congruency facilitation effect
on accuracy could be observed in angry voice stimuli, t(71) = 17.02, p < .001, Cohen’s d =
2.01. Further, there was no main effect of Group, F(1, 70) =
0.86, p = .356, η2p = 0.01, and no Group * Stimulus Condition interaction, F(2, 140) = 0.39, p
= .68, η2p = 0.005, on mean perceived intensity in attend voice trials. The main effect of
Stimulus Condition on mean perceived intensity in attend voice trials was highly significant,
F(2, 140) = 39.32, p < .001, η2p = 0.36, indicating both a congruency facilitation effect, t(71)
= 3.42, p = .003, Cohen’s d = 0.4, and an incongruency interference effect, t(71) = -5.44, p
< .001, Cohen’s d = -0.64, on intensity ratings in angry voice stimuli.

43
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
In sum, both groups overall showed similar mean RT, accuracy and mean intensity
ratings in both attend face and voice trials with target emotion angry, with the exception of
accuracy scores in attend voice trials, with the high proneness group being less accurate
compared to the low proneness group. Congruency facilitation and/or incongruency
interference effects could be observed for all measures in trials with target emotion angry in
both attention conditions, except for mean RT in attend face trials. Overall, both groups
showed a comparable pattern of in-/congruency effects for all measures in angry face and
voice trials. (see Figure 4 second row for mean RT, accuracy and mean perceived intensity for
target emotion angry).
Target Emotion Sad. Separate Group * Stimulus Condition mixed ANOVAs in attend
face trials with target emotion sad revealed neither a main effect of Group, F(1, 70) = 1.70, p
= .197, η2p = 0.02, nor of Stimulus Condition, F(2, 140) = 1.77, p = .175, η2p = 0.03, and no
Group * Stimulus Condition interaction, F(2, 140) = 1.12, p = .329, η2p = 0.02, on mean RT. A
mixed ANOVA on accuracy in attend face trials was not interpretable due to violations of
homogeneity of error variances (Levene-test p < .05). Post-hoc comparisons revealed a non-
significant trend for lower accuracy in the high proneness (M = 77.91, SD = 10.85) compared
to the low proneness group (M = 82.25, SD = 9.79) during categorization of sad face stimuli,
t(70) = -1.78, p = .079, Cohen’s d = -0.42. Both a congruency facilitation, t(71) = 4.4, p
< .001, Cohen’s d = 0.52, and a incongruency interference effect, t(71) = -6.5, p < .001,
Cohen’s d = -0.77, could be observed on accuracy in sad face stimuli. Further, there was no
main effect of Group, F(1, 70) = 0.01, p = .93, η2p = 0.001, and no Group * Stimulus
Condition interaction, F(1.78, 124.37) = 1.61, p = .206, η2p = 0.02, on mean perceived
intensity in attend face trials. The main effect of Stimulus Condition on mean perceived
intensity in attend face trials was highly significant, F(1.78, 124.37) = 21.03, p < .001, η2p =
0.23, indicating both a congruency facilitation effect, t(71) = 3.51, p = .003, Cohen’s d = 0.41,
and an incongruency interference effect, t(71) = -3.6, p = .002, Cohen’s d = -0.43, on intensity
ratings in sad face stimuli.
Separate Group * Stimulus Condition mixed ANOVAs in attend voice trials with target
emotion sad revealed no main effect of Group on mean RT, F(1, 70) = 0.21, p = .652, η2p =
0.003, and no Group * Stimulus Condition interaction, F(2, 140) = 0.42, p = .959, η2p = 0.001
(note: there was no homogeneity of covariances in mean RT in sad voice trials, Boxtest p

44
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
= .001, not allowing an interpretation of the interaction). There was a highly significant main
effect of Stimulus Condition on mean RT in attend voice trials, F(2, 140) = 17.16, p < .001, η2p
= 0.20, indicating an incongruency interference effect on mean RT in sad voice stimuli, t(71)
= 5.83, p < .001, Cohen’s d= 0.69. A mixed ANOVA on accuracy in attend voice trials was not
interpretable due to violations of homogeneity of error variances (Levenetest p < .05). Post-
hoc comparisons revealed a non-significant trend for lower accuracy in the high proneness (M
= 91.60, SD = 7.31) compared to the low proneness group (M = 94.40, SD = 5.66) during
categorization of sad voice stimuli, t(70) = -1.82, p = .073, Cohen’s d = -.043.
An incongruency interference effect on accuracy could be observed in sad voice stimuli, t(71)
= -6.21, p < .001, Cohen’s d = -0.73. Further, there was no main effect of Group, F(1, 70) =
0.14, p = .705, η2p = 0.002, and no Group * Stimulus Condition interaction, F(1.83, 128.3) =
0.15, p = .845, η2p = 0.002, on mean perceived intensity in attend voice trials. The main effect
of Stimulus Condition on mean perceived intensity in attend voice trials was highly
significant, F(1.83, 128.3) = 40.37, p < .001, η2p = 0.37, indicating an incongruency
interference effect on intensity ratings in sad voice stimuli, t(71) = -8.71, p < .001, Cohen’s d
= -1.03, as well as lower intensity ratings in congruent compared to unimodal sad voice trials,
t(71) = -3.95, p < .001, Cohen’s d = -0.47.
In sum, both groups showed similar mean RT and mean intensity ratings in trials with
target emotion sad in both attention conditions. However, the high proneness group showed a
non-significant trend for lower accuracy compared to the low proneness group in trials with
target emotion sad in both the attend face and attend voice condition. Congruency facilitation
and/or incongruency interference effects could be observed for all measures in trials with
target emotion sad in both attention conditions except for mean RT in attend face trials. Both
groups showed a similar pattern of in-/congruency effects for all measures in sad face and
voice trials (see Figure 4 third row for mean RT, accuracy and mean perceived intensity for
target emotion sad).
Target Emotion Neutral. Separate Group * Stimulus Condition mixed ANOVAs in
attend face trials with target emotion neutral revealed a non-significant trend for a main effect
of Group on mean RT, F(1, 70) = 3.15, p = .081, η2p = 0.04, indicating a non-significant trend
for lower mean RT in the high proneness (M = 1494.04, SD = 240.02) compared to the low
proneness group (M = 1613.13, SD = 316.63) when categorizing emotionally neutral face

45
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
stimuli. There was a highly significant main effect of Stimulus Condition on mean RT in
attend face trials, F(2, 140) = 8.97, p < .001, η2p = 0.12, indicating a congruency facilitation
effect on mean RT in emotionally neutral face stimuli, t(71) = -2.49, p = .024, Cohen’s d =
0.29. There was no Group * Stimulus Condition interaction on mean RT in attend face trials,
F(2, 140) = 1.79, p = .17, η2p = 0.03. Further, there was no main effect of Group, F(1, 70) =
2.59, p = .112, η2p = 0.04, and no Group * Stimulus Condition interaction, F(1.79, 125.2) =
0.59, p = .539, η2p = 0.008, on accuracy in attend voice face trials. The main effect of Stimulus
Condition on accuracy in attend face trials was highly significant, F(1.79, 125.2) = 8.64, p
< .001, η2p = 0.11, indicating a congruency facilitation effect on accuracy in emotionally
neutral face stimuli, t(71) = 4.06, p < .001, Cohen’s d = 0.48. There was a significant main
effect of Group on mean perceived intensity in attend face trials, F(1, 70) = 6.65, p = .012, η2p
= 0.09, indicating significantly higher intensity ratings of emotionally neutral faces in the high
proneness (M = 3.35, SD = 0.64) compared to the low proneness group (M = 2.91, SD = 0.77).
The main effect of Stimulus Condition on mean perceived intensity was significant, F(1.84,
128.78) = 4.48, p = .016, η2p = 0.06, indicating a congruency facilitation effect on intensity
ratings in emotionally neutral face stimuli, t(71) = 3.42, p = .003, Cohen’s d = 0.4. There was
no Group * Stimulus Condition interaction on mean perceived intensity in attend face trials,
F(1.84, 128.78) = 0.65, p = .512, η2p = 0.009.
Separate Group * Stimulus Condition mixed ANOVAs in attend voice trials with target
emotion neutral revealed a non-significant trend for a main effect of Group on mean
RT, F(1, 70) = 3.50, p = .066, η2p = 0.05, indicating a non-significant trend for lower mean
RT in the high proneness (M = 1585.00, SD = 281.4) compared to the low proneness group (M
= 1711.25, SD = 291.15) during categorization of emotionally neutral voice stimuli. There
was a highly significant main effect of Stimulus Condition on mean RT in attend voice trials,
F(2, 140) = 11.84, p < .001, η2p = 0.15. Group and Stimulus Condition interacted significantly
with each other on mean RT, F(2, 140) = 5.70, p = .004, η2p = 0.08. Post-hoc comparisons
revealed lower mean RT in the high proneness compared to the low proneness group in
incongruent, t(70) = -2.98, p = .004, Cohen’s d = -0.7, but not in unimodal, t(70) = -0.87, p =
.414, Cohen’s d = -0.19, or congruent neutral voice trials, t(70) = -1.26, p = .212, Cohen’s d =
0.30. The high proneness group showed a congruency facilitation, t(35) = -2.28, p = .029,

46
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Cohen’s d = -0.38, but no incongruency interference effect, t(35) = -0.41, p = .681, Cohen’s d
= -0.07, on mean RT in neutral voice trials, whereas the low proneness group showed an
incongruency interference, t(35) = 4.2, p < .001, Cohen’s d = 0.7, but no congruency
facilitation effect, t(35) = -0.9, p = .374, Cohen’s d = -0.15. There was no main effect of
Group on accuracy in attend voice trials, F(1, 70) = 0.07, p = .797, η2p = 0.001. There was a
highly significant main effect of Stimulus Condition, F(2, 140) = 11.86, p < .001, η2p = 0.15,
and a non-significant trend for a Group * Stimulus Condition interaction, F(2, 140) = 2.83, p =
.062, η2p = 0.04, on accuracy in attend voice trials. Post-hoc comparisons revealed similar
accuracy for both groups in unimodal, t(70) = -0.77, p = .442, Cohen’s d = -0.18, congruent,
t(70) = -1.13, p = .262, Cohen’s d = -0.27, and incongruent neutral voice trials, t(70) = 0.97, p
= .335, Cohen’s d = 0.23. The high proneness group showed neither a congruency facilitation,
t(35) = -0.02, p = .982, Cohen’s d = -.004, nor an incongruency interference effect, t(35) =
1.36, p = .183, Cohen’s d = -0.23, on accuracy in neutral voice trails, whereas the low
proneness group showed an incongruency interference, t(35) = -4.21, p < .001, Cohen’s d =
0.7, but no congruency facilitation effect, t(35) = 0.61, p = .549, Cohen’s d = 0.1. Due to
violations of homogeneity of error variances (Levene-test p < .05), a mixed ANOVA on mean
perceived intensity was not interpretable. Post-hoc comparisons revealed a non-significant
trend for higher intensity ratings of emotionally neutral voice stimuli in the high proneness (M
= 3.32, SD = 0.67) compared to the low-proneness group (M = 2.98, SD = 0.85), t(70) = 1.9, p
= .061, Cohen’s d = 0.45. Further, an incongruency interference effect on mean perceived
intensity could be observed in emotionally neutral voice stimuli, t(71) = -3.14, p = .008,
Cohen’s d = -0.37.
In sum, the high proneness group showed a non-significant trend for lower mean RT in
trials with target emotion neutral in both the attend face and attend voice condition as well as
higher intensity ratings in attend face and a non-significant trend for higher intensity ratings in
attend voice trials with target emotion neutral. Overall, accuracy scores were similar in both
groups in trials with target emotion neutral in both attention conditions. Congruency
facilitation and/or incongruency interference effects could be observed for all measures in
trials with target emotion neutral in both attention conditions. The low proneness group
showed a marked incongruency interference effect on mean RT in neutral voice trials,
whereas the high proneness group did not show this effect. Further, the high proneness group
did not show any in-/congruency effects on accuracy in neutral voice trials, in contrast to the
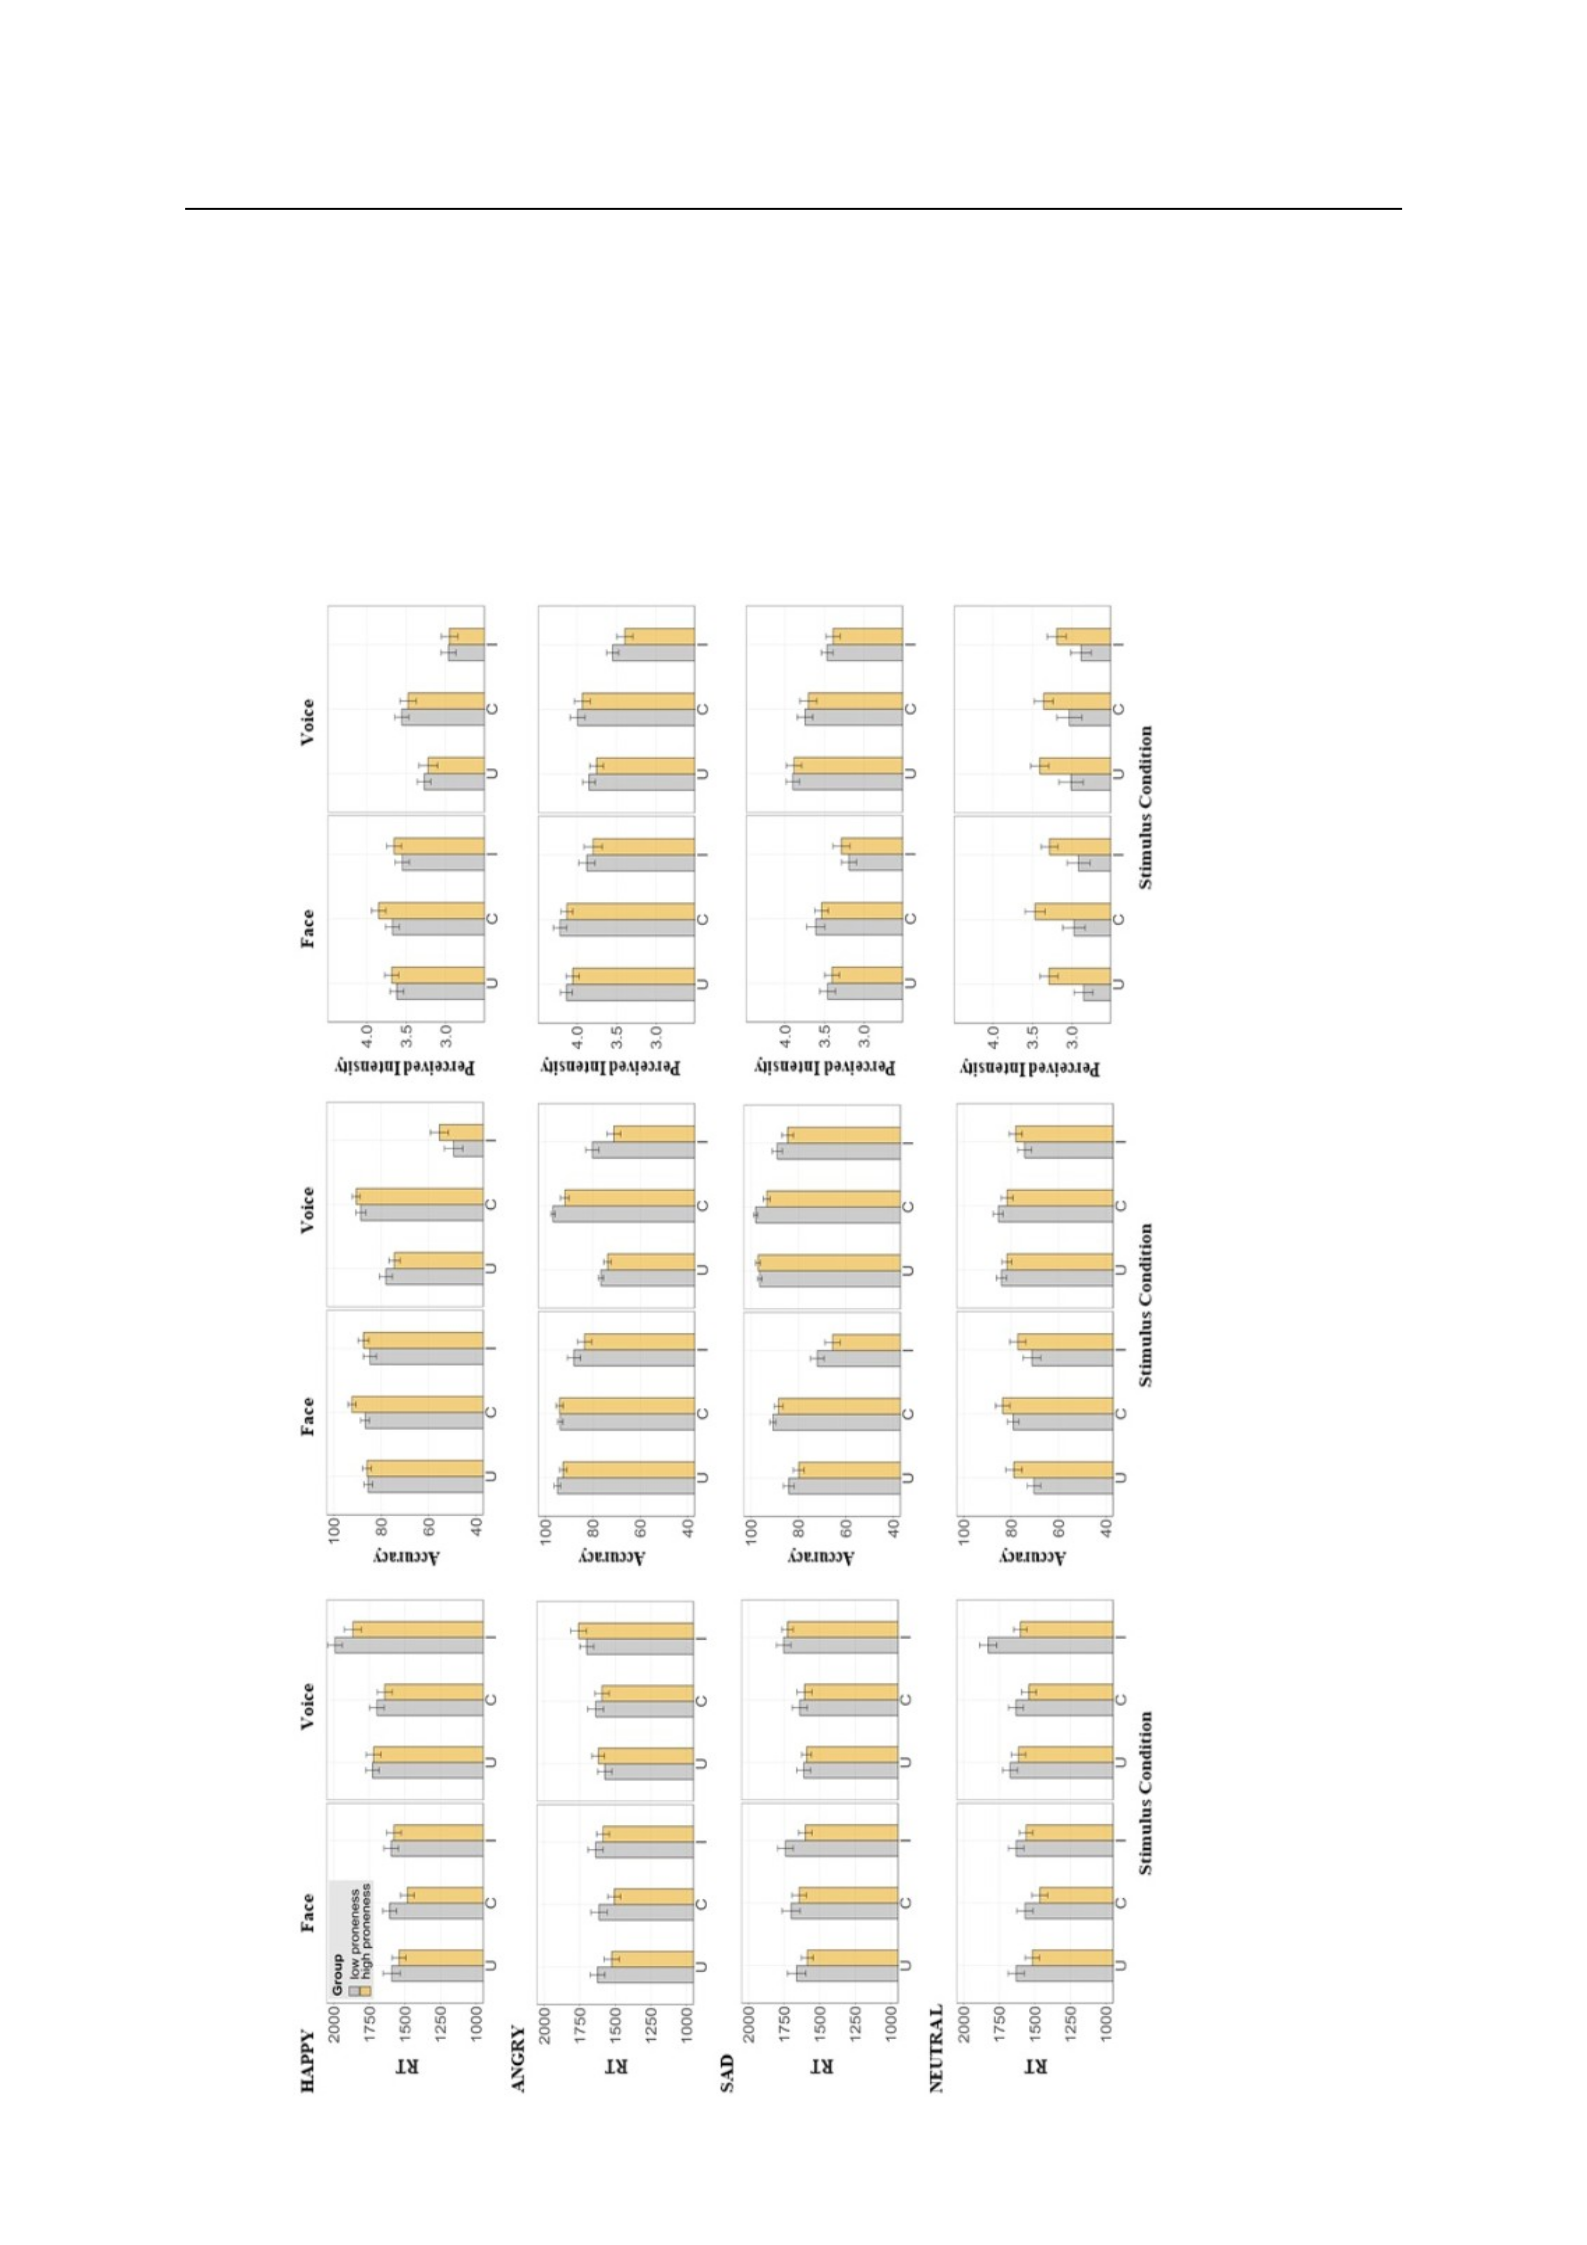
47
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
low proneness group (see Figure 4 bottom row for mean RT, accuracy and mean perceived
intensity for target emotion neutral).
l Intensity for each Target Emotion per Group and Stimulus Condition, Separated by
Notes. n
low
= 36, nhigh
= 36. Error bars denote ±1 standard error of the mean. Face = attend face trial
congruent; I = bimodal emotionally incongruent.

48
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
3.2 Control Variables and Questionnaire data
3.2.1 Control Tests for Attention, Processing Speed, and Vigilance
TMT. Mean completion time (in seconds) in the TMT-A version was similar in the high
proneness (M = 30.1, SD = 10.9) and the low proneness group (M = 27.0, SD = 8.0), t(70) = -
1.36, p = .178, Cohen’s d = 0.32. Further, the high proneness (M = 54.1, SD = 13.7) and low
proneness group (M = 54.9, SD = 16.5) showed similar mean completion time in the TMT-B
version, t(70) = 0.22, p = .824, Cohen’s d = - 0.05.
CPT-IP. The 2 (Group) x 3 (Digit Load) mixed ANOVA for CPT-d’-scores revealed a
significant main effect of Digit Load, F(2, 140) = 269.53, p < .001, η2p = 0.79, indicating
higher d’-values in the 2-digit load condition (M = 3.80, SD = 0.47) compared to both the
3digit load condition (M = 2.84, SD = 0.84), t(71) = 10.26, p < .001, and the 4-digit load
condition (M = 1.63, SD = 0.73), t(71) = 23.45, p < .0001, as well as higher d’-values in the
3digit load condition compared to the 4-digit load condition, t(71) = 12.86, p < .001. There
was no main effect of Group, F(1, 70) = 0.36, p = .55, η2p = 0.005, and no Group * Digit Load
interaction, F(2, 140) = 0.48, p = .618, η2p = 0.007.
3.2.2 Questionnaire Data
CAPS. Groups significantly differed in CAPS total scores, with the high proneness
group showing higher scores (M = 11.3, SD = 6.4) compared to the low proneness group (M =
5.7, SD = 4.3), t(61.52) = 4.31, p < .001, Cohen’s d = 1.02.
LSHS. Groups significantly differed in LSHS-E total scores, with the high proneness
group showing higher scores (M = 15.3, SD = 9.7) compared to the low proneness group (M =
8.6, SD = 7.1), t(70) = 3.39, p = .001, Cohen’s d = 0.80.
PCL3. Groups did not significantly differ in PCL total scores, with the high proneness
group showing a non-significant trend towards higher scores (M = 47.3, SD = 27.1) compared
to the low proneness group (M = 34.8, SD = 26.3), t(70) = 1.98, p = .052, Cohen’s d = 0.47.
BCSS. Groups did neither differ in BCSS negative self scores (high proneness: M =
4.2, SD = 3.1; low proneness: M = 3.3, SD = 2.7), t(70) = 1.34, p = .185, Cohen’s d = 0.32, nor
in BCSS negative other scores (high proneness: M = 4.8, SD = 3.3; low proneness: M =
3.8, SD = 3.9), t(68.5) = 1.17, p = .246, Cohen’s d = 0.28.
3 One subject in the low and one in the high proneness group had ≥50% missings in the PCL. Their PCL scores
were corrected by the respective group mean.

49
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Correlations Between Questionnaire Scores. Bonferroni-corrected Pearson
correlation coefficients over all subjects revealed highly significant moderate to strong
correlations between CAPS and LSHS, between CAPS and PCL, between LSHS and PCL,
and between PCL and both BCSS negative subscales, all r > .4 and p < .001. Further, there
was a significant correlation between LSHS and BCSS negative other subscale, r = .40, p
< .05. No other correlation between questionnaires scores reached statistical significance, all p
> .05 (see Table 2 for Pearson’s r for correlations of questionnaire data).
3.3 Correlations Between Experimental Data and Questionnaire Data
3.3.1 Correlations Between IE Difference Scores and Questionnaire Data
Pearson correlation coefficients over all subject indicated small negative correlations
between the IE difference score congruent-unimodal in attend face trials and the CAPS (r
= .24, uncorrected p = .046) as well as between the IE difference score congruent-incongruent
in attend voice trials and the BCSS negative other scale (r = -.23, uncorrected p = .049).
Neither did survive Bonferroni-correction. No other correlation between IE difference scores
and questionnaire data reached statistical significance, all r < .3 and p > .05 (see Table 2 for
Pearson’s r for correlations between IE difference scores and questionnaire data).
3.3.2 Correlations Between IE Scores and Questionnaire Data
Pearson correlation coefficients over all subjects indicated negative correlations
between IE scores in congruent trials during attend face blocks and both the CAPS (r = -.33,
uncorrected p = .005) and LSHS (r = -.24, uncorrected p = .043), respectively. Neither did
survive Bonferroni-correction, Bonferroni-corrected p = .15 and p = 1. No other correlation
between IE scored and questionnaire data reached statistical significance, all r < .3 and p > .05
(see Table B.1 in Appendix B for Pearson’s r for correlations between IE scores and
questionnaire data).
4 Discussion
In this study, we investigated potential impairments in emotional MSI in stages prior
to psychosis onset. Following up on findings of altered emotional MSI in patients with the
diagnosis of a psychotic disorder (Lin et al., 2020; Tseng et al., 2015), we examined emotional
MSI in psychosis proneness in order to generate hypotheses regarding a potential role of
impaired emotional MSI for disorder development. Two groups of a healthy community
sample, one with low and the other with high psychosis proneness, categorized the perceived

50
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
emotion and rated the perceived emotional intensity of unimodal, bimodal emotionally
congruent and bimodal emotionally incongruent dynamic facial expressions and vocal
prosody. Over the course of 12 experimental blocks, the attended, i.e. task-relevant, modality
alternated, while the respective other modality had to be ignored (Föcker et al., 2011). Further,
participants completed neuropsychological tests for processing speed, attention, and vigilance
as well as self-report questionnaires for psychotic experiences and beliefs about the self and
others.
In both attention conditions, both groups showed comparable patterns of emotion
categorization performance and intensity ratings depending on stimulus congruency. This
indicated similar emotional MSI in our high and low psychosis proneness samples. These
results will be discussed in more detail in the following with regard to our hypotheses and
previous findings on emotional processing in psychosis and psychosis proneness.
4.1 Hypothesis 1: Crossmodal Modulation in Emotional MSI and Psychosis Proneness
4.1.1 Discussion and Comparison to Previous Evidence
We expected our high proneness sample to show aberrant crossmodal congruency
facilitation and incongruency interference effects during emotion categorization, which would
indicate atypical emotional MSI. In contrast to our expectation, our behavioral data did not
reveal an interaction between group and stimulus condition on categorization performance: In
both attention conditions, both groups showed lower IE scores (i.e. better performance) in
emotionally congruent stimuli and higher IE scores (i.e. worse performance) in emotionally
incongruent stimuli compared to unimodal stimuli, respectively. This indicates similar
congruency facilitation and incongruency interference effects in categorization performance
for both groups. Additionally, our data did not reveal a main effect of group on categorization
performance, indicating overall functional categorization of emotionally laden face and voice
stimuli in both groups. In sum, our findings suggest typically developed emotional MSI in our
psychosis proneness sample.
The analyses for mean perceived intensity ratings mirrored the findings of the
IEanalyses: we observed similar congruency facilitation and incongruency interference on
intensity ratings in both groups. Additionally, high and low psychosis proneness subjects
showed similar overall levels of mean perceived emotional intensity in both attention
conditions. The supplementary analyses for mean RT and accuracy provided analogue results:

51
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
overall, congruency and incongruency effects could be observed in terms of lower RT and
better accuracy in congruent trials as well as higher RT and lower accuracy in incongruent
trials compared to unimodal trials. In sum, we observed crossmodal modulation on intensity
ratings, RT, and accuracy for both the low and the high proneness group during processing of
emotionally laden AV stimuli, analogue to the results regarding IE.
Taken together, we were able to observe previously published crossmodal modulation
effects in emotional MSI (e.g. Collignon et al., 2008; Föcker et al., 2011; Föcker & Röder,
2019), successfully replicating the findings in subjects from the general population originally
published by Föcker et al., (2011) and in a further adoption of the original paradigm (Fengler
et al., 2017). We observed congruency facilitation and incongruency interference effects both
in emotion categorization and emotional intensity ratings in both attentions conditions, despite
the explicit instruction to ignore the task-irrelevant modality. This indicated that the
taskirrelevant, non-attended information, i.e. the facial or vocal cue, modulated the processing
of emotionally laden face expressions and vocal prosody, respectively. Thus, our findings are
consistent with previous work on crossmodal modulation in emotional MSI (e.g. Collignon et
al., 2008) and suggest that AV emotional MSI might constitute a bi-directional, automatic
process relatively independent of attentional focus (Fengler et al., 2017; Föcker et al., 2011;
Föcker & Röder, 2019).
Our results suggest typically developed emotional MSI in our psychosis proneness
sample, which differs from the majority of findings in patients with the diagnosis of a
psychotic disorder. Thus, our findings indicate a different pattern of emotional MSI in
psychosis proneness compared to studies in patients with the diagnosis of a psychotic
disorder. Previous studies had reported reduced crossmodal modulation by non-target
modality cues (de Gelder et al., 2005, Exp.1; de Jong et al., 2009; Fiszdon & Bell, 2009;
Seubert, 2010), reduced AV emotion matching performance (Castagna et al., 2013; Jeong et
al., 2021), or lower emotion categorization performance in AV trials (Giannitelli et al., 2015;
Mangelinckx et al., 2017; Thaler et al., 2013) in patients compared to healthy controls.
Further, Müller et al. (2014) and Portnova et al., (2021) reported altered ERP responses during
processing of AV emotional stimuli in patients compared to healthy controls, especially when
visual and auditory cues were incongruent, possibly reflecting deficient neural responses to
conflicting AV emotional information in psychosis.

52
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Further, our findings in psychosis proneness also show a different pattern compared to
patient studies reporting excessive emotional MSI: both de Gelder et al. (2005, Exp.2) and
Van den Stock et al. (2011) reported an increased crossmodal modulation by the non-target
modality on AV emotion categorization in patients compared to controls. However, the
subjects in the study by Van den Stock et al. (2011) had to categorize the perceived emotion in
body expressions rather than facial expressions. It is possible that the specific stimulus
characteristics in facial vs. body expression recognition and potential discrepancies in the
respective task demand differently impact AV emotion recognition in psychosis. Strauss et al.
(2015) had indeed reported deficits in recognizing emotional body expression in patients with
the diagnosis of a psychotic disorder compared to healthy controls. To our knowledge,
however, no published study directly compared deficits in emotional face and body
expressions in psychosis.
On the other hand, our findings in psychosis proneness are in line with findings of
studies reporting similar AV emotion categorization performance (Müller et al., 2014;
Simpson et al., 2013; Zvyagintsev et al., 2013) and similar AV emotion valence ratings
(Sestito et al., 2013) in patients with the diagnosis of a psychotic disorder compared to healthy
controls, reflecting unimpaired behavioral performance during multisensory processing of
emotional face and voice stimuli.
Taken together, our findings might suggest that emotional MSI in psychosis proneness
remains mostly intact prior to disorder onset, with aberrances potentially manifesting later in
full-blown psychosis. Unlike multisensory emotion processing reported here, previous studies
have reported impairments in unisensory emotion processing in high psychosis proneness
(Seo et al., 2020; van Donkersgoed et al., 2015). It is possible that multisensory processes
ameliorate these unisensory emotion processing deficits, resulting in similar AV emotion
categorization in subjects with high and low proneness. Crossmodal compensatory effects
during processing of congruent crossmodal compared to unimodal emotional information, i.e.
at least partially intact crossmodal gains, have been reported in patients with the diagnosis of a
psychotic disorder (Mangelinckx et al., 2017; Müller et al., 2014; Simpson et al., 2013). It
could be speculated that psychosis proneness might be associated with relatively intact
crossmodal gain effects, which reduce with increased symptom load. Future research could
aim to disentangle whether a) psychosis proneness is associated with preserved crossmodal

53
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
gains ameliorating unisensory emotion processing deficits, b) if crossmodal gains change over
the course of disorder progression and c) which factors influence these changes. It is
important to note, however, that the lack of unisensory emotion processing differences
between our high and low proneness groups is inconsistent with reports of reduced facial and
vocal emotion recognition and discrimination in high psychosis proneness (Seo et al., 2020;
van Donkersgoed et al., 2015) and thus does not offer support for our speculation of preserved
crossmodal gains ameliorating unisensory emotion processing deficits in psychosis proneness.
4.1.2 A Potential Role of Disorder Progress Stage
Our sample mainly consisted of university students, who likely showed high levels of
emotional and social functioning and thus potentially preserved emotion processing
capabilities. Previous studies on unisensory emotion processing focused on individuals with
ultra-high risk for psychosis (Seo et al., 2020; van Donkersgoed et al., 2015). Thus, it is
possible that our sample did not exhibit similar levels of symptom load as well as
perceptualcognitive impairments as the subjects in previous studies. The lack of group
differences in processing speed, attention and vigilance in our data, which have been
previously reported to be impaired in psychosis proneness (Mesholam-Gately et al., 2009;
Nuechterlein et al., 2004), might support this assumption. However, our sample was allocated
to the high proneness group by means of a cut-off score in the CAPE (Stefanis et al., 2002),
which has been previously shown to distinguish between low and high proneness subjects
(Krkovic et al., 2020). Further, our high proneness group reported significantly higher levels
of anomalous perceptual experiences and psychotic symptoms compared to the low proneness
group. It is possible that both unisensory and multisensory emotion processing impairments
manifest rather in ultra-high risk states and full-blown psychosis than in psychosis proneness.
This is supported by studies reporting that age, illness duration and symptom severity
influence emotion processing deficits in psychosis (Edwards et al., 2002; Kohler et al., 2010)
and by studies reporting associations between impaired face and voice processing and higher
levels of perceptual-cognitive dysfunctions and psychotic symptoms (Darke et al., 2021; Lin
et al., 2018). On the other hand, unisensory emotion processing deficits in terms of impaired
facial affect recognition were already observed in subjects with increased genetic risk for
psychosis such as first-degree relatives of patients with the diagnosis of a psychotic disorder
(D. Martin et al., 2020), suggesting early impairments and a potential vulnerability marker for
psychosis (Seo et al., 2020). Further research is necessary to disentangle the development of

54
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
uni- and multisensory emotion processing deficits in psychosis proneness, ultra-high risk
groups and psychosis.
4.1.3 Attention Effects
In our exploratory analyses with attention condition as an additional factor, we
observed an interaction between group and attention condition, reflecting that the difference in
emotion categorization performance between attend face and attend voice trials was larger in
high proneness compared to low proneness subjects. This could suggest larger sensitivity to
emotional face expressions compared to vocal prosody in our high proneness subjects. While
we observed a group * attention condition interaction on IE scores, there was no such
interaction on mean perceived emotional intensity ratings. This suggests that a potentially
higher sensitivity to emotional face expressions compared to vocal prosody in high proneness
subjects might influence crossmodal emotion categorization but not the perception of
emotional intensity. The impact of visual vs. auditory modality on emotion recognition in
psychosis has not been sufficiently studied and experimental designs and results of previous
studies appeared to be too inconsistent for clear conclusions (Dondaine et al., 2014). Further,
to our knowledge no published study compared visual and auditory emotion recognition in
psychosis proneness. A study by Dondaine et al. (2014) aimed to compare visual and auditory
emotion recognition impairments in patients with the diagnosis of a psychotic disorder, but
did not observe an impact of modality on emotion recognition. However, Thaler et al. (2013)
observed different patterns of emotion misclassification in psychosis for affectively neutral
stimuli depending on presentation modality, i.e. visual, auditory or AV. More research
comparing visual and auditory emotion recognition deficits in psychosis and psychosis
proneness is needed to further investigate a potential role of task-relevant modality.
Further, we observed a significant interaction between attention and stimulus condition
in our exploratory 3-way analysis, indicating better categorization performance in attend face
compared to attend voice trials in the unimodal and the emotionally incongruent condition.
This suggests better face expression than vocal prosody recognition and less incongruency
interference of auditory cues when attending face compared to voice stimuli. The lack of
performance differences between attend face and attend voice trials in the emotionally
congruent condition could reflect greater crossmodal gain of face stimuli when attending
vocal prosody, resulting in similar performance as when attending face stimuli with

55
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
emotionally congruent vocal prosody. These findings might reflect visual dominance in
emotion recognition of dynamic face and voice stimuli and is consistent with previous studies
reporting a higher influence of emotional face stimuli compared to vocal stimuli when
categorizing emotions (e.g. Collignon et al., 2008).
4.1.4 Effects of Emotion Category and Valence
Our exploratory analysis of RT, accuracy and mean perceived intensity separately for
each of the four emotion categories revealed hints regarding a more fine-grained pattern of AV
emotion processing in our proneness sample. Our high proneness sample was less accurate in
categorizing angry voice stimuli compared to the low proneness group and showed non-
significant trends for less accurate categorizations of both sad face and voice stimuli. In
contrast, both groups showed similar categorization performance in happy face and voice
trials. Our findings are consistent with previous studies on emotion recognition deficits in
psychosis reporting pronounced deficits in categorizing negative emotions compared to
positive emotions (Bonfils et al., 2020; Tripoli et al., 2022; Won et al., 2019). Negative
emotion recognition deficits have been observed in early disorder stages (Won et al., 2019)
and it has been discussed that specific impairments in the recognition of negative emotions
such as anger might be associated with a higher vulnerability for psychosis (Tripoli et al.,
2022). A meta-analysis on emotion perception and functional outcomes in psychosis observed
an association between deficient emotion recognition and poor social skills such as social
problem solving (Irani et al., 2012). This could suggest that poor emotion recognition might
facilitate stressful social encounters and in turn exacerbate psychotic symptoms. However, the
meta-analysis did not distinguish between emotions of positive vs. negative valence. It could
be speculated that a pronounced deficit in recognizing negative emotions might be particular
impactful, since it can be assumed that social situations in which others express negative
emotions might be more stressful. Dysfunctional emotion recognition and a deficit in social
skills might lead to a particular stressful social encounter for the individual suffering from
psychosis, with detrimental consequences for their social behaviour and experience of
psychotic symptoms. Initial support for our speculation of a pronounced impact of deficient
negative emotion recognition can be found in a study by Modinos et al. (2020) in subjects
with high risk for psychosis, who observed an association between deficient anger and fear
recognition and poorer functional outcomes in terms of larger impairments in daily life. More

56
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
studies on a potentially specific impact of impaired negative emotion recognition on social
stress and psychotic experience are needed to corroborate our speculation.
Further, our high proneness group showed trends for faster categorization responses in
affectively neutral face and voice stimuli as well as higher intensity ratings in affectively
neutral face and a trend for higher intensity ratings in affectively neutral voice stimuli
compared to the low proneness group. This might suggest a heightened sensitivity or greater
attentional capture by affectively neutral stimuli in our high proneness sample, resulting in
faster responses. Further, affectively neutral information might have elicited overly high levels
of arousal in our high proneness subjects. This is consistent with previous studies reporting
aberrant processing of affectively neutral information in patients with the diagnosis of a
psychotic disorder (e.g. Dondaine et al., 2014; Garcia-Leon et al., 2021; Mitrovic et al., 2020;
Pinkham et al., 2011) and high psychosis proneness (Seo et al., 2020), suggesting that
psychosis might be associated with a greater sensitivity to affectively neutral stimuli. This
might also be reflected by aberrant neurophysiological responses towards neutral stimuli, such
as neural hyperactivity in frontal regions during emotion processing tasks, in psychosis (Lakis
& Mendrek, 2013; Modinos et al., 2015; Underwood et al., 2015) and psychosis proneness
(for a review, see Kozhuharova et al., 2020). It has been discussed that subjects with psychotic
symptoms misattribute affective meaning to neutral cues (e.g. Kohler et al., 2003; Mitrovic et
al., 2020), which is consistent with an erroneous attribution of salience to motivationally
irrelevant information in psychosis due to a dopaminergic dysfunction (Howes & Kapur,
2009). This so-called dopamine hypothesis states that an increased salience attribution and
insufficient filtering of irrelevant stimuli caused by dysregulated dopamine release and the
following biased cognitive interpretation of the resulting perceptual anomalies facilitate the
emergence of psychotic symptoms (Howes & Kapur, 2009; Howes & Murray, 2014). Further,
it has been discussed that mis-labeling of neutral faces as negative might at least partly be the
consequence of reduced visual scanning patterns of salient facial features for emotion
recognition observed in psychosis (for a review, see Toh et al., 2011) and psychosis proneness
(Hillmann et al., 2015, 2017). The vigilance-avoidance hypothesis assumes that psychosis,
especially paranoia, is associated with an attentional bias avoiding threat-related features in
facial cues to reduce arousal (Green et al., 2000; Green & Phillips, 2004). The interpretation
of the resulting ambiguous experience might then be influenced by a jumping-to-conclusion
bias (Freeman, 2016), increased threat expectation (Reininghaus et al., 2016) and the own

57
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
predominant emotional state of anxiety (Freeman, 2007). Hillman et al., (2018) argue that
these mechanisms might provide a theoretical link between psychotic symptoms and affective
misattribution to affectively neutral faces as well as negative mislabeling of neutral face
stimuli observed in psychosis (e.g. Mitrovic et al., 2020; Pinkham et al., 2011).
We observed interactions/non-significant trends for interactions between group and
stimulus condition on RT and accuracy in happy, angry and neutral trials, especially in the
attend voice condition. While the overall pattern of in-/congruency effects was observable in
both groups, the effects of simultaneously presented emotionally in-/congruent stimuli of the
unattended modality differed between groups in some cases. Numerically, it seemed that the
high proneness group showed smaller in-/congruency effects in affectively neutral attend
voice trials compared to the low proneness group. Further, it appeared as the low proneness
group showed similar RT in happy face trials regardless of stimulus condition, i.e. no
in/congruency effects, whereas the high proneness group showed a congruency facilitation
effect. This could suggest a ceiling effect in the low proneness group, reflecting that it was
sufficiently easy to recognize happy faces for low proneness subjects that additional vocal
cues had not further impact on RT.
It is important to note that we observed (trends for) group * stimulus condition
interactions mainly in attend voice trials. It is possible that emotion-specific MSI deficits in
psychosis proneness depend on the target modality, potentially reflecting modality dominance
effects. This is consistent with previous studies suggesting that the influence of the unattended
modality differed depending on the target modality in psychosis. Earlier studies indicated that
the impact of facial expressions on vocal prosody recognition was increased in patients
compared to healthy controls (de Gelder et al., 2005; de Jong et al., 2010) whereas the
influence of emotional vocal prosody on facial emotion recognition was reduced (de Gelder et
al., 2005). In contrast, de Jong et al. (2009) reported a reduced impact of facial expression on
emotional vocal prosody recognition. In sum, empirical evidence regarding potential modality
dominance aberrances on AV emotional MSI in psychosis is inconsistent and does not support
clear conclusions if modality dominance aberrances are specific for psychosis. Future research
should specifically investigate the influence of the target modality regarding the crossmodal
impact of the unattended modality on AV emotion recognition in psychosis.

58
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
Our emotion-specific results and especially the observed (trends for) interactions
should be interpreted with caution, since the original paradigm adopted from Föcker et al.
(2011) was not designed for such fine-grained approaches. The resulting trial numbers per
group * emotion category * attention condition * stimulus condition are small, hampering
robust statistical testing. Therefore, these results should be considered rather as hints for
future research regarding emotion-specific MSI deficits in psychosis proneness. To our
knowledge, our study is the first to follow such a fine-grained approach of emotional MSI in
subjects with psychotic symptoms. In previous studies, emotion-specific deficits in unisensory
emotion processing have been reported in psychosis (Barkl et al., 2014; Bonfils et al., 2019,
2020; Mitrovic et al., 2020; Tripoli et al., 2022; Won et al., 2019). It is possible that aberrant
patterns of emotional MSI in both patients and possibly psychosis proneness samples manifest
particularly for those emotions, which have been found to show pronounced unisensory
processing deficits, e.g. for negative and affectively neutral stimuli (Bonfils et al., 2020;
Dondaine et al., 2014; Mitrovic et al., 2020; Seo et al., 2020; Tripoli et al., 2022; Won et al.,
2019). Future research should specifically address potential emotion-specific patterns of
emotional MSI in psychosis proneness and patient samples. Initial evidence for
emotionspecific differences in multisensory compared to unisensory emotion processing can
be found in a study by Thaler et al. (2013), who observed a positive misattribution of AV
neutral stimuli in contrast to a negative misattribution of visual neutral stimuli. The authors
suggest that the additional auditory information in crossmodal trials crucially impacted the
misattribution valence, since auditory neutral stimuli were also positively misattributed
(Thaler et al., 2013). This highlights the above mentioned potential role of modality effects on
emotional MSI in psychosis. It is possible that interactions between modality effects and
specific emotion categories, e.g. negative and neutral information, play a role in the
manifestation of emotional MSI deficits in psychosis.
4.2 Associations between Emotional MSI and Psychotic Symptoms
4.2.1 Discussion and Comparison to Previous Evidence
Our second aim consisted of investigating potential associations between emotional
MSI and psychotic symptoms, such as perceptual anomalies and hallucinatory or paranoid
experiences. We expected significant correlations between in-/congruency effects in emotional
categorization and self-reported anomalous perceptual experiences, hallucinatory events, and
paranoid convictions. We further expected correlations between in-/congruency effects and

59
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
negative schemata about the self and others, since negative beliefs have been discussed to
influence the (psychotic) interpretation of aberrant perceptual experiences (Garety et al.,
2001). After multiple comparison correction, we did not observe any significant correlation
between IE difference scores and questionnaire scores in CAPS, LSHS-E, PCL and BCSS
negative subscales. Thus, our analysis did not reveal any association between in/congruency
effects during emotional categorization of AV stimuli and self-reported experience of
perceptual anomalies, hallucinations, paranoia and negative schemata.
In our exploratory correlation analysis between IE scores and questionnaire data, we
observed a small, negative Pearson correlation between IE scores during categorization of
emotionally congruent stimuli in the attend face condition and CAPS scores with a correlation
coefficient r = -.33 and an uncorrected p = .005, which however did not survive multiple
comparison, Bonferroni-corrected p = .15. It is possible that our study was underpowered and
therefore unable to detect a statistically significant association. However, we were only able to
observe this one potentially meaningful association between IE scores and questionnaires
instead of a broader pattern reflecting systematic associations between AV emotion
categorization and psychotic symptoms in our sample. Our results do not support clear
conclusions about association patterns between psychotic symptoms in our proneness sample
and AV emotion processing. Future, larger-scale studies should develop hypotheses based on
this hint in our results regarding associations between psychotic symptoms and processing of
emotional faces with emotionally congruent vocal prosody. Given a well-designed future
study, it could be speculated to potentially reveal that the higher the self-reported occurrence
of perceptual anomalies, the better the categorization performance of emotional face
expression with simultaneously presented emotionally congruent prosody. However, even if a
larger-scale study would reveal a statistically significant correlation, it remains questionable
which theoretical conclusions regarding AV emotion processing in psychosis proneness might
be drawn from this isolated correlation. To date, it could be at best discussed to reflect a
potential small processing benefit for emotionally congruent AV information in persons with
higher occurrence of aberrant perceptual phenomena.
Only few studies on emotional MSI in psychosis investigated associations between
multisensory emotion recognition and positive or negative symptoms. The majority of studies
failed to observe correlations between emotional MSI and positive or negative symptoms

60
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
(Giannitelli et al., 2015; Jeong et al., 2021; Mangelinckx et al., 2017; Müller et al., 2014;
Seubert, 2010), and only one study revealed an association to negative symptoms (Castagna et
al., 2013). However, both Müller et al. (2014) and Portnova et al. (2021) reported associations
between symptom severity and aberrant neural responses to AV emotional stimuli. This could
suggest that deficient MSI might not show associations to specific symptoms of psychosis but
rather to general symptom severity. It is possible that we failed to observe associations to
psychotic symptoms, since we focused on positive symptoms rather than severity of
symptoms associated with psychosis.
4.2.2 Associations to Positive vs. Negative Symptoms and a Role of Stimulus Complexity
Previous studies on unisensory emotion processing in psychosis reported associations
between facial emotion recognition deficits and negative symptoms (e.g. Edwards et al., 2001;
Fakra et al., 2015; Turetsky et al., 2007). It is possible that we were unable to observe
associations between AV emotion processing deficits and psychosis proneness because we
focused on positive rather than negative symptoms. However, a recent review revealed
associations between emotion recognition deficits of face expressions and negative symptoms
whereas vocal prosody recognition showed associations with positive symptoms, suggesting a
role of presentation modality (Lin et al., 2020). Further, Darke et al. (2021) observed
associations between positive symptoms such as delusions and facial emotion processing
deficits and argue that specific stimulus characteristics might have a crucial impact. Previous
studies reporting associations to negative symptoms used static face stimuli, while Darke et al.
(2021) and Johnston et al. (2010) observed associations to positive symptoms using dynamic
face stimuli. Thus, association patterns between positive or negative symptoms and emotion
processing deficits might differ depending on whether presented face stimuli are static or
dynamic (Darke et al., 2021; Johnston et al., 2010).
It is possible that the usage of dynamic vs. static face stimuli has an impact on
processing crossmodal emotional information in psychosis and on revealing associations
between psychotic symptoms and deficient emotional MSI. The majority of previous studies
on emotional MSI in patients with the diagnosis of a psychotic disorder used static rather than
dynamic face stimuli (Castagna et al., 2013; de Gelder et al., 2005; de Jong et al., 2009, 2010;
Giannitelli et al., 2015; Mangelinckx et al., 2017; Müller et al., 2014; Portnova et al., 2021;
Seubert, 2010; Zvyagintsev et al., 2013), whereas only a subgroup of studies used dynamic

61
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
voice stimuli (Fiszdon & Bell, 2009; Sestito et al., 2013; Simpson et al., 2013; Thaler et al.,
2013). However, within both stimuli categories results of previous studies are inconsistent,
with patients showing either deficient or unimpaired emotional MSI and only very few studies
reporting associations to symptoms of psychosis.
4.3 Limitations and Implications for Future Research
In addition to limitations of our study already mentioned earlier, e.g. the recruitment of
a possibly high-functional sample and a potential lack of statistical power for correlation and
emotion-specific analyses, following potential limitations and implications for future studies
should be discussed.
Patients with the diagnosis of a psychotic disorder and persons with psychosis
proneness showed a negativity bias in unisensory emotion processing (Pinkham et al., 2011;
Seo et al., 2020), which might be associated with increased paranoia and greater difficulties in
social situations (Pinkham et al., 2011). In our study, we focused on overall emotional MSI in
psychosis proneness and explored emotion-specific patterns of crossmodal emotion
recognition, analyzing correctly classified stimuli analogue to the analysis strategy by Föcker
et al. (2011). As mentioned earlier, our experimental paradigm adopted by Föcker et al. (2011)
restricted our possibilities for statistical testing regarding emotion-specific patterns, especially
regarding statistically meaningful analyses of incorrect emotion classifications. It would be
interesting to investigate whether our proneness sample showed a negativity bias in
incorrectly classified emotional stimuli, i.e. misclassified stimuli as negatively valenced.
Future studies should investigate whether a negativity bias can also be observed during
multisensory emotion recognition both in patient and proneness samples.
A further potential limitation of our study might consist in the restriction to the
emotion categories happy, angry, sad and neutral. Previous studies reported impaired
processing of fearful stimuli and a bias to mislabel emotional cues as fearful in psychosis (e.g.
Garcia-Leon et al., 2021; van Dijke et al., 2016). Further, the recognition of fearful face
expressions seemed to be already particularly impaired in early stages of disorder progression
- contrary to the recognition of other emotions, which rather seemed to deteriorate over the
course of disorder development - and it has recently been suggested that impaired fear
recognition in particular might be a vulnerability marker for psychosis (Pena-Garijo et al.,
2023). Future implementations of emotional MSI paradigms in psychosis proneness should

62
CHAPTER II: EMOTIONAL MULTISENSORY INTEGRATION IN PSYCHOSIS
PRONENESS
include fearful stimuli and investigate if psychosis proneness is associated with particular
deficits in the recognition of fearful AV stimuli.
4.4 Conclusion
In conclusion, our findings do not offer support for the hypothesis that deficient
emotional MSI might play a role in the development of psychotic disorders. Studies reporting
unisensory emotion processing deficits in psychosis proneness assumed a potential predictive
role of emotion processing deficits for symptom development and disorder progression
(Corcoran et al., 2015; D. Martin et al., 2020; Seo et al., 2020; Tripoli et al., 2022; Tseng et
al., 2016). Based on our findings and as mentioned throughout the discussion of the literature,
it likely requires a more nuanced approach to study the interplay of both unisensory and
multisensory emotion processing in the developmental trajectory from psychosis proneness to
psychosis. Specifically, future studies on emotion processing in psychosis should take
additional influential factors such as specific emotion categories, modality effects, symptom
severity (Lin et al., 2020), or stimulus characteristics such as static vs. dynamic cues (Darke et
al., 2021) and their potential interactions into account.

63
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
Chapter III:
Temporal Multisensory Integration &
Crossmodal Temporal Recalibration
in Psychosis (Study 2)

64
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
1 Introduction
1.1 Temporal Multisensory Processing
In everyday life, we receive a multitude of environmental and self-related information at
any time point, with the temporal characteristics of incoming cues forming a temporal
relationship. The temporal dynamics of stimuli, such as their temporal synchrony, are a central
feature determining whether crossmodal stimuli should be perceptually integrated or not
(Meredith et al., 1987; Stein & Meredith, 1993). The appropriate temporal ordering of events
and judgements whether events are synchronous or not are crucial for the construction of a
coherent percept and subsequent adaptive behaviour.
Uni- and crossmodal stimuli have been found to be integrated with a higher likelihood,
if their stimulus onset asynchrony (SOA), i.e. the temporal delay between their respective
onset, falls within in a so-called temporal binding window, TBW (Chen & Vroomen, 2013;
Vroomen & Keetels, 2010; Wallace & Stevenson, 2014). Stimuli with a SOA smaller than this
TBW are judged to likely belong to the same event due to their temporal alignment and
perceptually integrated, a process called temporal MSI, and stimuli with a SOA larger than the
TBW as belonging to different events (Wallace et al., 2020; Wallace & Stevenson, 2014). The
TBW varies per subject (Stevenson et al., 2012; Wallace & Stevenson, 2014) and is narrower
for simple stimuli such as arbitrary flashes and tones and wider for complex information such
as speech (Vroomen & Keetels, 2010; Wallace & Stevenson, 2014).
Apart from the on-line integration of crossmodal temporal stimuli, the perceptual
system also is able to adapt to temporal asynchronies of crossmodal stimuli, a phenomenon
called crossmodal temporal recalibration (for reviews, see Chen & Vroomen, 2013; Vroomen
& Keetels, 2010). For example, repeated exposure to a fixed temporal asynchrony between
AV stimuli shifts the point of subjective simultaneity (PSS) of a following temporal order
judgement (TOJ) or SJ of the AV stimuli in direction of the temporal asynchrony (Fujisaki et
al., 2004; Vroomen et al., 2004). This cumulative crossmodal recalibration has been observed
between various modality combinations such as AV, audio-tactile or visuo-tactile stimuli as
well as in sensorimotor cues and both in simple and complex stimuli such as speech (Chen &
Vroomen, 2013). It has been discussed that the perceptual system adapts to crossmodal
asynchronies, caused e.g. by different physical signal transmission and arrival time or neural
processing speed, due to a tendency to reduce discrepancies between the various sensory
modalities (Simon et al., 2018; Vroomen & Keetels, 2010). In addition to this cumulative
temporal recalibration building up by continuous exposure to a crossmodal asynchrony,

65
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
previous studies have observed rapid temporal recalibration occurring already after a single
exposure to a crossmodal asynchrony (e.g. Van der Burg et al., 2013, 2015). For example, the
PSS during a SJ task of an AV trial has been observed to shift in direction of the leading
modality on the immediately preceding AV trial, indicating an immediate temporal
recalibration effect induced by the immediate stimulus history (Van der Burg et al., 2013).
Immediate temporal recalibration might benefit multisensory processing in a highly dynamic
environment with continuously changing temporal relations between stimuli: a rapid
adjustment to crossmodal asynchronies might facilitate MSI processes, since crossmodal gain
is expected to be maximal during crossmodal synchrony (Van der Burg et al., 2015).
Further, the cumulative and immediate temporal recalibration effects have been
discussed to reflect separate processes. A study by Van der Burg et al. (2015) successfully
observed both effects in a SJ paradigm with prior exposure to AV asynchronies. The authors
reported that cumulative recalibration was maximal directly after repeated asynchrony
exposure and declined over time, whereas immediate recalibration changed trial-by-trial and
seemed unaffected by the magnitude of cumulative recalibration. Van der Burg et al. (2015)
argued that this suggested a relative independence of both recalibration processes and
potentially indicated different mechanisms.
Studies in the spatial domain suggested that, although MSI and crossmodal
recalibration are separate processes, both seemed to be at least partly related. Park & Kayser
(2019) observed shared neural substrates in medial parietal regions of spatial MSI and
immediate crossmodal recalibration, suggesting a link between both multisensory processes.
Further, a study by Rohlf et al. (2020) observed MSI and immediate recalibration in children
of seven years, whereas cumulative recalibration was only observed in later age groups. The
authors proposed that MSI and immediate recalibration processes develop earlier in life
compared to cumulative recalibration and speculated that especially MSI might be a process
necessary for the development of cumulative recalibration (Rohlf et al., 2020). Bruns et al.,
(2022) demonstrated that congenital-cataract subjects, who were born blind and regained
vision through surgery later in life, showed intact MSI and immediate recalibration, but
atypical cumulative recalibration. Crucially, MSI correlated significantly with immediate
recalibration (Bruns et al., 2022), a finding which was also observed in the study by Rohlf et
al. (2020). In sum, previous evidence suggested that MSI and immediate crossmodal
recalibration might be related multisensory processes, whereas cumulative recalibration
develops later and potentially relies on functional development of especially MSI but also

66
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
immediate recalibration (Bruns et al., 2022; Rohlf et al., 2020). It is important to note,
however, that the evidence suggesting such links (Bruns et al., 2022; Park & Kayser, 2019;
Rohlf et al., 2020) focused on the spatial rather than the temporal domain. More research is
needed to investigate if analogue links between temporal MSI and crossmodal temporal
recalibration might exist.
In sum, the brain uses information about the temporal dynamics of environmental and
self-related stimuli to constantly order perceptual events, judge whether stimuli stem from the
same source and recalibrate for small temporal discrepancies (Chen & Vroomen, 2013;
Meredith et al., 1987; Stein & Meredith, 1993). A failure in appropriate temporal integration
and recalibration of crossmodal stimuli might drastically impair the construction of a coherent
percept and the ability to adapt to a constantly changing environment, which might facilitate
perceptual-cognitive disintegration phenomena in neurodevelopmental disorder such as
psychosis (Hornix et al., 2019; Postmes et al., 2014; Uhlhaas & Mishara, 2006).
1.2 Psychosis, Time Perception and Temporal Processing
There has been considerable work on time perception and temporal processing in
psychosis. Numerous studies reported that psychosis is associated with a wide range of time
processing impairments, with patients with the diagnosis of a psychotic disorder showing
altered time perception, such as overestimation of time periods or difficulties in rhythm
detection, and deficient temporal processing, such as poorer performance in SJ or TOJ tasks,
compared to healthy controls (for reviews, see Amadeo et al., 2022; Ciullo et al., 2016;
Thoenes & Oberfeld, 2017).
It has been reported that time perception was accelerated in psychosis, possibly due to
a hyperfunction of an internal pace maker (Ueda et al., 2018). This pace maker is thought to
regulate time perception and processing by emitting pulses used for e.g. estimation of time
periods (Hartcher-O’Brien et al., 2016). Crucially, the internal pace maker is thought to be
regulated via the dopamine system (Cheng et al., 2007), which has been found to be
dysregulated in psychosis (Howes & Kapur, 2009; Kapur, 2003), suggesting a connection
between hypervigilance in psychosis and aberrant time processing mechanisms (Ueda et al.,
2018).
It has been proposed that a dysfunction in the perception and processing of temporal
information constitutes a core deficit in psychosis (e.g. Amadeo et al., 2022; Andreasen et al.,
1999) and that psychotic symptoms might be the consequence of impaired temporal

67
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
organization of information processing (Thoenes & Oberfeld, 2017). The model of cognitive
dysmetria proposes that dysfunctional temporal information processing in psychosis might
trigger a detrimental cascade of effects, such as inappropriate temporal linking of external and
internal cues, hampering the formation of coherent percepts and facilitating the emergence of
psychotic symptoms (Andreasen et al., 1999). Support for a connection between psychotic
symptoms and impaired time processing comes from a recent meta-analysis reporting an
association between positive symptoms in psychosis and impaired performance on timing
tasks (Ueda et al., 2018). Further, dysfunctional time perception and temporal processing have
also been observed in individuals with psychosis proneness and high genetic risk for
psychosis, suggesting a potential endophenotype for psychosis (Amadeo et al., 2022).
1.3 Temporal Multisensory Processing in Psychosis
Aberrances in temporal MSI in psychosis have been reported in previous studies, with
patients with the diagnosis of a psychotic disorder showing an enlarged TBW during temporal
multisensory processes compared to healthy controls (Noel et al., 2018; for a review and
meta-analysis, see Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021). This
enlargement of the TBW in psychosis has also been reported within unisensory modalities,
with an enlargement in the range of tens of milliseconds (Amadeo et al., 2022). For
crossmodal stimuli however, the enlargement of the TBW increases up to hundreds of
milliseconds (Amadeo et al., 2022), suggesting pronounced impairments in multisensory
compared to unisensory temporal processing. This is supported by a study of Stevenson, Park
et al. (2017), who reported that AV SJ performance deficits in patients with the diagnosis of a
psychotic disorder were larger than impaired performance within visual or auditory
modalities. Further, enlargements of the TBW in psychosis might be pronounced in speech
compared to simple stimuli (Foucher et al., 2007; Noel et al., 2018), indicating a possible
influence of stimulus complexity and suggesting potentially detrimental consequences for
communication.
Impaired temporal multisensory processing in terms of an enlarged TBW has been
discussed to represent a potential core deficit in psychosis and already in stages prior to
disorder onset, e.g. in psychosis proneness (Amadeo et al., 2022). This is supported by
findings of Stevenson, Park et al. (2017), who observed that an enlarged TBW predicted
hallucination severity in patients with the diagnosis of a psychotic disorder. Further, several
studies reported associations between an enlarged TBW and higher schizotypy as well as

68
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
symptoms such as disorganization and hallucinations in psychosis proneness (Dalal et al.,
2021; Di Cosmo et al., 2021; Ferri et al., 2017, 2018; Marsicano et al., 2022).
An enlarged TBW might form a sensory-perceptual basis for psychosis and facilitate the
development of psychotic symptoms (Zhou et al., 2018). An enlarged TBW in psychosis
might lead to integration of crossmodal stimuli, which would not be integrated in healthy
controls. Inappropriate temporal integration of sensory input might facilitate insufficient
information filtering and ambiguous perception (Sartorato et al., 2017), leading to deficits in
organizing sensory information into coherent percepts (Uhlhaas & Mishara, 2006) and to
psychotic symptoms such as hallucinations (Stevenson, Park, et al., 2017) and self-disorders
(Postmes et al., 2014).
1.4 Crossmodal Temporal Recalibration in Psychosis and other Neurodevelopmental
Disorders
While there has been considerable work on unisensory and multisensory temporal
processing in psychosis (for reviews, see Amadeo et al., 2022; Ciullo et al., 2016; Thoenes &
Oberfeld, 2017; Wallace et al., 2020; Wallace & Stevenson, 2014; Zhou et al., 2018), to our
knowledge studies investigating crossmodal temporal recalibration in psychosis are extremely
scarce.
Initial evidence regarding crossmodal temporal recalibration in patients with the
diagnosis of a psychotic disorder can be found in a study by Zhou, Cui, et al. (2022). Using an
SJ paradigm with simple AV stimuli and AV speech stimuli, Zhou, Cui, et al. (2022) observed
that adolescent patients with the diagnosis of EOS showed a similar magnitude of immediate
temporal recalibration compared to age-matched controls. While this suggested that early-
onset psychosis might be associated with intact recalibration of SJ to the immediate stimulus
history, generalizability to adult-onset psychosis4 might be drastically limited. EOS is a
particularly rare form of psychosis (Driver et al., 2013) and has been found to exhibit
significantly higher symptom load as well as premorbid cognitive impairments (e.g. Vyas et
al., 2011), suggesting that the disorder trajectory and perceptual-cognitive deficits might not
be entirely comparable to adult-onset psychosis. Further, multisensory temporal processing
performance varies with age (Noel et al., 2016), with reports of immediate temporal
recalibration being observed in adults both in simple and speech stimuli but not adolescents,
4 Whenever the terms „psychosis“ or “diagnosis of a psychotic disorder” are mentioned throughout this chapter,
they refer to adult-onset psychosis. EOS/early onset psychosis will be mentioned as such to distinguish both
disorder manifestations.

69
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
who only showed recalibration in speech stimuli (Zhou et al., 2020). Thus, conducting a
crossmodal temporal recalibration paradigm in adult patients with the diagnosis of adult-onset
psychotic disorder is necessary to a) eliminate age-related confounding factors on
multisensory temporal processing and b) collect evidence on both cumulative and immediate
temporal recalibration in the more commonly encountered adult-onset psychosis as opposed
to the highly rare EOS.
Although autism spectrum disorders (ASD) and psychosis compose distinct disorders
with different clinical manifestations, it has been discussed that both disorders might be partly
related (e.g. King & Lord, 2011) with ASD and psychosis sharing similarities e.g. in neural
connectivity impairments (Friston et al., 2016; Just, 2004) or genetic factors (Carroll & Owen,
2009). Further, previous work suggested that ASD and psychosis share dysfunctions in uni-
and multisensory processes (Wallace et al., 2020; Wallace & Stevenson, 2014; Zhou et al.,
2018). Patients with the diagnosis of an ASD have been found to show comparable
impairments in temporal multisensory processes as patients with the diagnosis of a psychotic
disorder, such as an enlarged TBW in crossmodal stimuli (Wallace & Stevenson, 2014; Zhou
et al., 2018). Given these overlaps between both neurodevelopmental disorders, studies
investigating crossmodal temporal recalibration in ASD might give further hints for
hypothesis generation of potential crossmodal temporal recalibration alterations in psychosis.
A study by Turi et al. (2016) investigated immediate temporal recalibration in autism
and observed that adult patients with the diagnosis of an ASD showed little to no immediate
recalibration in a SJ task compared to healthy controls. Both Noel, De Niear et al. (2017) and
Zhou, Cui, et al. (2022) extended these findings to samples consisting of children and
adolescents with the diagnosis of an ASD, reporting reduced immediate temporal recalibration
in SJ tasks to immediately preceding asynchronies in ASD compared to agematched control
groups. Another study by Stevenson, Toulmin, et al. (2017) observed an association between
increased autistic traits and a reduced size of the cumulative recalibration effect in a SJ task in
a healthy student sample. This suggested that symptoms of ASD might be associated with
decreased cumulative temporal recalibration (Stevenson, Toulmin, et al., 2017). In sum, prior
evidence indicated that ASD might be associated with deficient immediate and cumulative
temporal recalibration, which adds to previously published evidence regarding deficits in
temporal MSI in ASD (Zhou et al., 2018).

70
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
In sum, previous studies reported dysfunctional unisensory and multisensory temporal
processing in psychosis (e.g. Amadeo et al., 2022; Thoenes & Oberfeld, 2017; Zhou et al.,
2018) and altered crossmodal temporal recalibration in ASD (Noel, De Niear, et al., 2017;
Stevenson, Toulmin, et al., 2017; Turi et al., 2016; Zhou, Cui, et al., 2022), a disorder
demonstrating comparable deficits in temporal MSI compared to psychosis (Zhou et al.,
2018). Further, it has been discussed that MSI and crossmodal recalibration might be partly
related processes at least in the spatial domain (Bruns et al., 2022; Park & Kayser, 2019;
Rohlf et al., 2020). Thus, it can be speculated that crossmodal temporal recalibration is altered
in psychosis. Altered or dysfunctional cumulative and immediate temporal recalibration
processes might have detrimental effects for the perceptual adaptation to natural temporal
asynchronies and impair the formation of coherent percepts of the environment and the self.
1.5 Research Questions
The aim of this study was to investigate if psychosis is associated with impaired
crossmodal temporal recalibration during an SJ task. Further, we intended to replicate earlier
findings of an increased TBW window in simple AV stimuli in psychosis (Zhou et al., 2018;
Zhou, Lai, et al., 2022). Finally, we aimed to reveal associations between impaired
multisensory temporal processing (i.e. both integration and recalibration) and psychotic
symptoms, thereby extending previous findings which had focused on associations between
an enlarged TBW and psychotic symptoms in patients and psychosis proneness (Dalal et al.,
2021; Di Cosmo et al., 2021; Ferri et al., 2017, 2018; Foucher et al., 2007; Marsicano et al.,
2022; Stevenson, Park, et al., 2017).
Patients with the diagnosis of psychotic disorder and healthy controls judged if AV
stimuli presented with varying SOAs appeared simultaneously in several SJ test phases.
Before each SJ test phase, the same AV stimuli were presented with a fixed temporal lag - half
of the phases a visual lead adaptation phase, the other half auditory lead - to induce
cumulative temporal recalibration, i.e. a change in PSS depending on the modality order of
the previous adaptation phase. Further, immediate temporal recalibration was assessed by
examining the PSS of SJ responses depending on the modality order of the immediately
preceding SJ trial (paradigm adopted from Van der Burg et al., 2015).
We expected the patient group to showed a wider distribution of positive SJ responses
compared to healthy controls, i.e. to judge AV stimuli as simultaneous more often in larger
SOAs, indicating an enlarged TBW. Further, based on findings in ASD (Noel, De Niear, et al.,

71
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
2017; Turi et al., 2016; Zhou, Cui, et al., 2022), we expected altered crossmodal temporal
recalibration in psychosis: We expected the patient group to show a smaller difference in PSS
between visual lead adapted SJ trials and auditory lead adapted SJ trials compared to controls,
indicating altered cumulative temporal recalibration. We also expected the patient group to
show a smaller PSS-difference between SJ trials immediately preceded by a visual first SJ
trial and preceded by an auditory first SJ trial compared to healthy controls, indicating altered
immediate temporal recalibration. Finally, we expected the TBW, the cumulative, and the
immediate temporal recalibration effect to show associations with self-reports about
anomalous perceptual experiences, hallucinations, delusions, passivity experiences and
negative schemata about the self and others.
2 Methods
2.1 Participants
28 patients with the diagnosis of a psychotic disorder and 27 healthy controls originally
enrolled in the study. Patients were recruited via flyers in outpatient clinics and social care
centers as well as contact data bases from earlier studies with consent for further contact,
healthy controls via online recruitment services from the University of Hamburg. Two patients
discontinued the participation. We further had to exclude one patient from statistical analysis
due to random response behavior in the experimental task (see 2.4 Data Analysis). The final
sample therefore consisted of 25 patients with the diagnosis of a psychotic disorder and 27
healthy controls. Groups did neither differ in age, t(49.4) = 1.02, p = .31, Cohen’s d = 0.28,
nor regarding the distribution of gender, Χ2(1) = 1.90, p = .168, φ = 0.19, but differed in
distribution of education level, Χ2(3) = 9.51, p = .023, φ = 0.43 (see Table 3 for demographic
data).
The inclusion criteria for patients were defined as the Diagnostic and Statistical Manual
for Mental Disorders (DSM-V; American Psychiatric Association, 2022) criteria fulfillment
for schizophrenia or schizoaffective disorder. Patient-specific exclusion criteria consisted of a
comorbid autism spectrum disorder. Exclusion criteria for healthy controls consisted of a past
or present psychiatric disorder or a family history of first degree relatives with the diagnosis
of a psychotic disorder. General exclusion criteria were defined as dementia or other
neurological disorders, acute suicidality, substance abuse disorder in the last 6 months,
uncorrected sight or hearing impairment as well as inability to give consent or understand
study instructions due to health status or language barriers.

72
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
Prior to participation, informed consent was discussed with participants and obtained in
written form. Further, participation was compensated by 10€/hour or course credits. The study
was performed by the standards of the Declaration of Helsinki and was approved by the Local
Ethics Committee of the Faculty of Psychology and Human Movement Science, University of
Hamburg.
Table 3
Demographic and Diagnostic Data Separated by Group
Patients Healthy Controls
n 25 27
Age, M (range) 41.2 (23-63) 37.9 (21-63)
Gender, n (%)
female
male
diverse
10 (40)
15 (60)
0
17 (63.0)
10 (37.0)
0
Education, n
9 years
10 years 12-13
yearsa
university degreeb
0
7
15
3
1
4
9
13
CAPS, M (SD) 11.6 (5.8) 1.4 (2.0)
LSHS-E, M (SD) 24.3 (11.9) 3.2 (4.1)
PCL, M (SD) 94.2 (52.3) 26.0 (26.2)
Passivity experiences, M (SD) 7 (4.5) 0.1 (0.5)
BCSS n.S., M (SD) 6.6 (4.5) 2.0 (2.5)
BCSS n.O., M (SD) 9.8 (5.6) 3.5 (3.8)

73
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
Notes. N = 52. CAPS = Cardiff Anomalous Perception Scale, total score; LSHS-E = Launey-Slade Hallucination
Scale-Extended, total score; PCL= Paranoia Checklist, total score; BCSS n.S. = Brief Core Schema Scales,
negative self subscale; BCSS n.O. = Brief Core Schema Scales, negative other subscale.
a due to changes in German education law in 2007, the years of education for acquire the Abitur (A-level/high
school equivalent) vary between 12-13 years depending on school and Bundesland; b university degree: Bachelor
level or higher.
2.2 Stimuli and Experimental Paradigm
The experimental paradigm was adopted from Van der Burg et al. (2015). Stimuli were
presented and participants’ behavioural data recorded by means of the Neurobs Presentation®
Software (Version 22; Neurobehavioural Systems Inc., Berkeley, California, USA).
The experiment took place in a dimly-lit room. Participants were seated in front of a
computer screen (61cm diameter, screen resolution: 1920 x 1200), resting their head on a chin
rest at 40cm distance to the screen. Over the course of the whole experiment, a white fixation
dot was continuously presented in the center of the black screen. Visual stimuli consisted of a
white ring (radius 2.6° and width 0.4° visual angle, duration 50ms), which was presented in
the screen center. The auditory stimulus consisted of a sinusoidal tone (500Hz, duration 50ms
with 0.5ms rise and fall time) and was presented via headphones (Sennheiser HD 65TV,
Sennheiser electronic GmbH & Co. KG, Wedemark, Germany).
The paradigm consisted of five blocks: a pretest block and four experimental blocks,
each with alternating adaptation and SJ test phases. In adaptation phases, both the visual and
auditory stimulus were presented with a fixed SOA of ±200ms, followed by an Inter-
TrialInterval (ITI), which randomly varied from 650 - 850ms in 50ms steps. AV adaptation
trials were repeated 235 times per adaptation phase, resulting in a duration of approximately
3min for each adaptation phase. In half of the adaptation phases, the visual stimulus was
leading
(visual lead, SOA +200ms), in the other half the auditory stimulus was leading (auditory lead,
SOA -200ms). Within each of the four experimental blocks, one visual lead and one auditory
lead adaptation phase was presented. For half of the participants, each experimental block first
contained a visual lead and then an auditory lead adaptation phase and vice versa for the other
half of participants. Participants were asked to pay attention to both stimuli while fixating the
white fixation dot.
Within each experimental block, each adaptation phase was followed by a SJ test
phase, resulting in two adaptation conditions: visual lead adapted test trials and auditory lead

74
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
adapted test trials. In test phases, both the visual and auditory stimuli were presented with a
varying SOA (0, ±64, ±128, ±256 or ±512ms, with positive SOAs reflecting visual stimulus
first trials). Each SOA condition was presented multiple times, with the smaller SOA
conditions (i.e. 0, ±64) being presented 28 times each and the larger (i.e. ±128, ±256 or
±512ms) 14 times each, resulting in 98 test trials per test phase. Immediately following
stimulus presentation, participants were asked to indicate per button press if AV stimuli were
synchronous or not, i.e. give a SJ. Responses were given by means of response buttons, which
were placed left and right of the chin rest in comfortable position to be reached by the
participant. Each button was assigned one answer, i.e. “synchronous” vs. “not synchronous”
and the allocation to the left and right button was counterbalanced over participants. In SJ test
phases, the respective answer for each button was continuously presented at the bottom left
and bottom right of the computer screen. The visual stimulus always remained on screen until
the participant pressed a button, while the auditory stimulus was presented for 50ms.
Following the participant’s response, the next test trial started after an inter-trial-interval,
which randomly varied from 650 - 850ms in 50ms steps. The pretest block had the exact same
structure as one test phase.
At the beginning of each phase, the instruction of the phase type (adaptation or SJ test
phase) was presented at the center of the screen and participants started the phase by pressing
Enter on a custom keyboard. After each experimental block consisting of two adaptation and
two test phases in alternating order, participants could take a short break of 2-3 min before the
experimenter started the next experimental block. Breaks within a block were not allowed.
2.3 General Procedure
The study was split into two sessions, which took place on two different days. Each
session had a duration of about 1.25 to 1.5 hours.
In the session one, informed consent was discussed with participants, followed by
diagnostic procedures enquiring both in- as well exclusion criteria and data relevant for
analysis. Participants gave information about age, gender, education level, potential sight or
hearing impairment and respective corrections, potential psychiatric diagnoses and their
current status, illness duration of psychotic disorders, potential family history of psychotic
disorder, psychopharmacological medication, wakefulness, motivation, stress level and
substance consumption in the last 24 hours. Further, the Edinburgh Handedness Inventory

75
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
(EHI; Oldfield, 1971) was conducted measuring handedness, followed by the TMT Version A
and B (Reitan & Wolfson, 1985) for attention and processing speed. Following these shorter
diagnostic procedures, in- and exclusion criteria regarding psychiatric diagnoses were checked
by means of the Structural Clinical Interview for DSM-V (SCID-V; Beesdo-Baum et al.,
2019). For healthy controls, the sections A “Affective Disorders” and B “Psychotic Disorders”
were conducted, followed by a screening for the remaining sections. If the screening question
for a section was scored with “yes”, the respective section was conducted in full. In patients
with the diagnosis of a psychotic disorder, sections A and B were also conducted. Instead of
the screening, however, the Psychotic Symptom Rating Scales (PSYRATS; Haddock et al.,
1999) was administered to obtain further details regarding acoustic verbal hallucinations and
delusions. Finally, vigilance was measured by means of the Continuous Performance Test
Identical Pairs (CPT-IP; Nuechterlein et al., 2008)).
Participants were asked to provide self-reports about psychosis-related constructs
inbetween sessions. At the end of session one, participants received a questionnaire set
consisting of questions regarding usual substance consumption and the following
questionnaires: the BCSS (Fowler et al., 2006) for schemata about the self and others, the
CAPS (Bell et al., 2006) for anomalous perceptual experiences, the LSHS-E (Lincoln et al.,
2009; Siddi et al., 2019) for hallucinations, the PCL (Freeman et al., 2005) for paranoia and
questions for the factor bizarre experiences of the Community Assessment of Psychic
Experiences (Schlier et al., 2015; Stefanis et al., 2002) for passivity experiences (a glossary of
the instruments and questionnaires used in this dissertation project can be found in Table A.1
in Appendix A). Participants were asked to fill in the questionnaires at home and hand them
back at the second session. Potential questions regarding the questionnaire set were addressed
at the end of session two.
Depending on the participant’s individual schedule, session two took place within 1-10
days after session one. During session two, the experimental paradigm (see 2.2 Stimuli and
Experimental Paradigm) was conducted. Participants were comfortably seated in a chair in
front of the experimental computer placing their chin on the chin rest. Experimental
instructions were read to participants and potential questions clarified. The pretest block was
then started, followed by blocks one to four with short breaks in-between each block. The
experimenter remained in the experimental room and sat in a chair with a distance about 2.5

76
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
meters to the participant surveying the experimental progress. Following the experimental run,
participants were de-briefed and received participation compensation.
2.4 Data Analysis
The preprocessing steps of raw behavioral data were adapted from Van der Burg et al.
(2015). Data preprocessing and analysis was conducted using R Version 4.2.2 (R Core Team,
2022).
Prior to statistical analysis, we visualized each participant’s SJ response ratio relative
to each SOA to judge if the SJ responses relative to each SOA approximated a Gaussian
distribution. This was done for each of the following preprocessing steps with Gaussian fits:
for each participant, the actual SJ responses relative to each SOA and the curve of the
Gaussian fit were visualized in the same plot to detect random response behaviour. Based on
this procedure, one patient with random response behaviour was excluded from further
analysis.
To investigate potential group differences in overall SJ performance, we calculated the
percentage of correct SJ per participant over all SJ test trials and compared both groups by
means of a Welch two sample t-Test. Further, we fit a Gaussian distribution over all SJ test
trials with the parameters mean, bandwidth, and height per participant and defined the
bandwidth as an estimation of the general TBW. The TBW was compared between groups by
means of a Welch two sample t-test.
To investigate cumulative temporal recalibration, i.e. the effect of AV adaptation
phases on following SJ responses, we fit a Gaussian distribution with the parameters mean,
bandwidth, and height over the first 50 trials of SJ test phases per participant. Per adaptation
condition (visual lead adapted vs. auditory lead adapted), we pooled the first 50 test trials over
all 4 blocks, resulting in 200 trials per adaptation condition. We calculated a Group (patients
vs. healthy controls) * Adaptation Condition (visual lead adapted vs. auditory lead adapted)
mixed ANOVA on the mean of the Gaussian fit over the first 50 test trials as an estimation of
the PSS, followed by Bonferroni-corrected post-hoc t-tests. The Gaussian fit over the first 50
test trials per adaptation condition was chosen since we expected the cumulative recalibration
effect to be largest at the beginning of each test phase based on the results of Van der Burg et
al. (2015). The Greenhouse-Geisser correction (Greenhouse & Geisser, 1959) was applied in
case of sphericity violations.

77
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
To investigate immediate temporal recalibration, we fit a Gaussian distribution with
the parameters mean, bandwidth, and height over all SJ test trials per participant, separately
for test trials immediately preceded by a visual first (i.e. with an SOA > 0ms) vs. by an
auditory first (i.e. with an SOA < 0ms) test trial. The mean of the Gaussian fits was defined as
an estimate for the PSS and entered in a Group (patients vs. healthy controls) * Modality
order on t-1 (prior visual first vs. prior auditory first) mixed ANOVA, followed by
Bonferroni-corrected post-hoc t-tests. The Gaussian distribution was fit over all test trials
since we expected the immediate recalibration effect to be stable over course of the
experiment based on the results of Van der Burg et al. (2015).
We further investigated the time course of the cumulative and immediate recalibration
effects by fitting a Gaussian distribution with the parameters mean, bandwidth and height over
the respective SJ test trials for both recalibration effects (s.a.) in moving trial window bins of
50 trials each, starting with trials 1 to 50, fitting the Gaussian distribution, shifting the trial
window by one trial (i.e. 2 to 51), fitting and so on, resulting in 49 Gaussian fits. For each of
the 49 Gaussian fits, i.e. per trial window, we calculated the difference between the mean of
the fit, as an estimate of the PSS, over visually lead adapted minus the mean of the fit over
auditory lead adapted test trials for the cumulative recalibration effect, and between the mean
of the fit over test trials preceded by a visual first minus the mean of the fit over by an
auditory first test trial for the immediate recalibration effect. The respective PSS-difference
scores were then entered in FDR-corrected Welch two sample t-tests per trial window to
compare the groups at each time point, for both recalibration effects separately. Further, we
calculated FDR-corrected one-sample t-tests against zero per trial window separately for each
group for both recalibration effects.
Demographic data, i.e. age, gender, and education, was statistically compared between
groups by means of a Welch two sample t-test for age and Pearson Χ2-tests for gender and
education distribution, respectively.
TMT-A and -B completion times (in seconds) were each compared between groups by
means of Welch two sample t-tests to check for group differences in attention and processing
speed. Further, a Group (patients vs. healthy controls) * Digit Load (2 vs. 3 vs. 4 digits) mixed
ANOVA on CPT-IP d’ scores was conducted to check for group differences in vigilance,
followed by Bonferroni-corrected post-hoc t-tests. If group differences in TMT or CPT-IP
were revealed, a potential influence of the respective control variable on the TBW, the

78
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
cumulative, and the immediate recalibration effect was estimated. For the cumulative
recalibration effect, we calculated the PSS-difference in the first 50 visual lead minus auditory
lead adapted test trials. For the immediate recalibration effect, we calculated the
PSSdifference in test trials preceded by a visual first minus by an auditory first test trial.
Spearman’s rank correlation coefficients (ρ) with Bonferroni-corrected p-values were then
calculated between the TMT completion time scores and CPT-IP d’, respectively, and the
general TBW (defined as bandwidth over all trials), the cumulative recalibration effect in the
first 50 test trials, and the immediate recalibration effect.
Questionnaire scores, i.e. CAPS, LSHS-E, PCL, passivity experiences and BCSS
scores, were compared between groups by means of Welch two sample t-tests, separately for
each questionnaire.
Spearman rank correlation coefficients ρ with Bonferroni-corrected p-values were
calculated between experimental data (i.e. general TBW, the cumulative recalibration effect in
the first 50 test trials, and the immediate recalibration effect) and questionnaire scores to
investigate associations between TBW as well as cumulative and immediate temporal
recalibration and self-reports of psychosis-related constructs. For all correlation analyses,
Spearman rank correlation coefficients ρ > .3 were marked in correlation matrices and
regarded potentially considerable for further discussion.
Additionally, Bayesian hypothesis testing using standard priors in JASP Version 0.16.4
(Wagenmakers et al., 2018) was conducted analogue to the frequentist statistical tests for
experimental and questionnaire data described above, with Bayes Factors (BF) indicating
evidence in favor of the null or alternative hypothesis. BF are classified per convention as
follows: a BF of 1 is discussed to reflect no evidence, between 3-10 moderate, between 10100
strong, and >100 extreme evidence in favor of the alternative hypothesis. Accordingly, a BF
between 1/3-1/10 is discussed to reflect moderate, between 1/10-1/100 strong, and <1/100
extreme evidence in favor of the null hypothesis (an extensive BF classification scheme can
be found in Wagenmakers et al., 2018). We reported BF10 for two-tailed tests and correlations,
the BF describing evidence for the alternative relative to the null hypothesis, and BFincl for
mixed ANOVAS, the BF reflecting the posterior probability for model inclusion for a factor or
interaction term averaged over all candidate models (Wagenmakers et al., 2018).

79
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
3 Results
3.1 Experimental data
3.1.1 Percent of Correct SJ
Patients (M = 50.82, SD = 8.45) and healthy controls (M = 50.18, SD = 7.46) did not
differ in percentage of correct SJ, t(48.03) = 0.28, p = .773, Cohen’s d = 0.08, BF10 = 0.29.
3.1.2 TBW – Bandwidth over all Test Trials
The general TBW (defined as the bandwidth of the Gaussian fit over all test trials) did
not statistically differ between patients (M = 284.06, SD = 110.79) and healthy controls (M =
274.96, SD = 100.04), t(48.44) = 0.31, p = .758, Cohen’s d = 0.09, BF10 = 0.29 (see Figure 5
for the distribution of the TBW in both groups).
3.1.3 Cumulative Temporal Recalibration
A Group (patients vs. healthy controls) * Adaptation (visual lead adapted vs. auditory
lead adapted) mixed ANOVA revealed a significant main effect of Group, F(1, 50) = 4.71, p
= .035, η2p = 0.09, BFincl = 1.48, indicating that the overall PSS in the first 50 trials (defined as
the mean of the Gaussian fit over the first 50 test trials) differed between patients (M = 67.21,
SD = 48.33) and healthy controls (M = 42.7, SD = 32.09). Further, there was a significant
main effect of Adaptation, F(1, 50) = 5.04, p = .029, η2p = 0.09, BFincl = 1.63, indicating that
the PSS in the first 50 test trials differed between visual lead adapted (M = 63.31, SD = 47.59)
and auditory lead adapted (M = 45.66, SD = 53.57) test trials. There was no Group *
Adaptation interaction, F(1, 50) = 0.23, p = .631, η2p < 0.01, BFincl = 0.53.
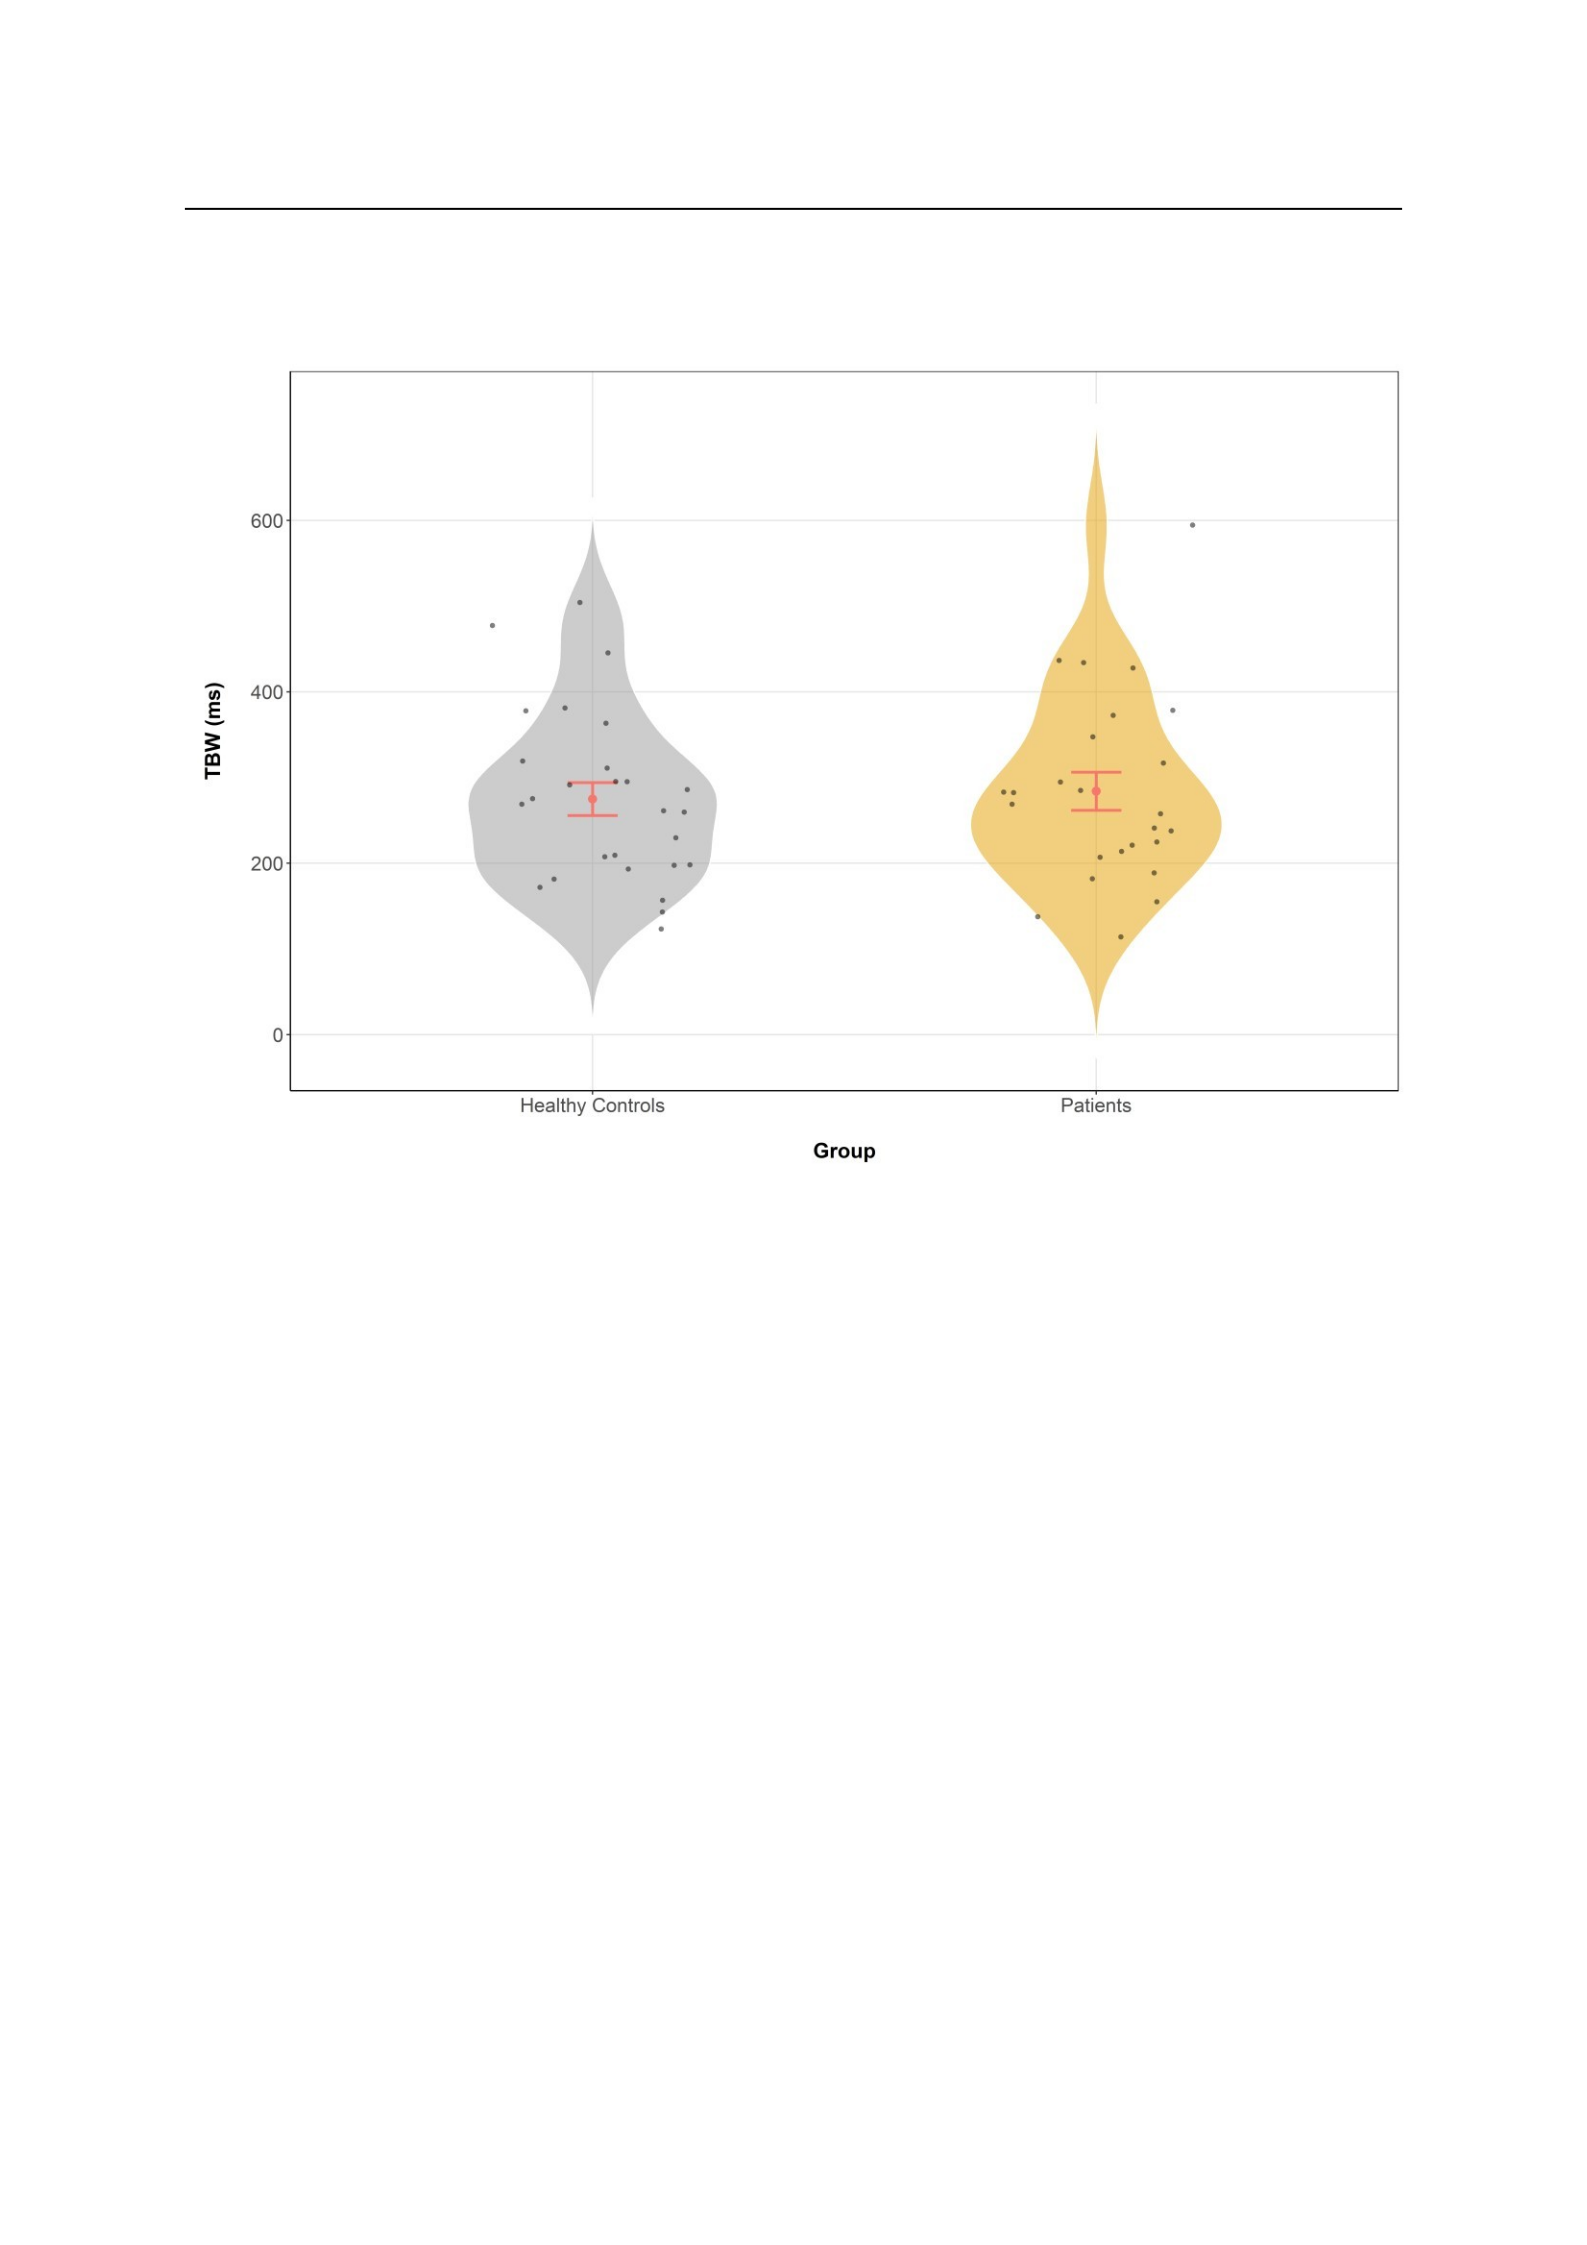
80
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
Figure 5
Distribution and Mean of Temporal Binding Window Values per Group
Notes. nPAT = 25; nHC = 27. TBW = temporal binding window. The general TBW was defined as the bandwidth of
a Gaussian fit over all test trials. Error bars denote ±1 standard error of the mean.
3.1.4 Immediate Temporal Recalibration
A Group (patients vs. healthy controls) * Modality order on t-1 (prior visual first vs.
prior auditory first) mixed ANOVA revealed a significant main effect of Group, F(1, 50) =
4.45, p = .040, η2p = 0.08, BFincl = 1.33, indicating that the overall PSS over all test trials
(defined as the mean of the Gaussian fit over all test trials) differed between patients (M =
61.74, SD = 42.27) and healthy controls (M = 38, SD = 38.86) . Further, there was a
significant main effect of Modality order on t-1, F(1, 50) = 10.91, p = .002, η2p = 0.18, BFincl =
21.26, indicating that the PSS (defined as the mean of the Gaussian fits over all test trials)
differed between test trials preceded by a visual first (M = 63.64, SD = 50.02) and an auditory
first (M = 35.20, SD = 53.81) test trial. There was no Group * Modality order on t-1
interaction, F(1, 50) = 0.02, p = .876, η2p < 0.01, BFincl = 0.61.
3.1.5 Time Course of Cumulative and Immediate Recalibration
Time Course of Cumulative Recalibration. There were no statistically significant
differences between groups in the PSS-difference between visual lead vs. auditory lead
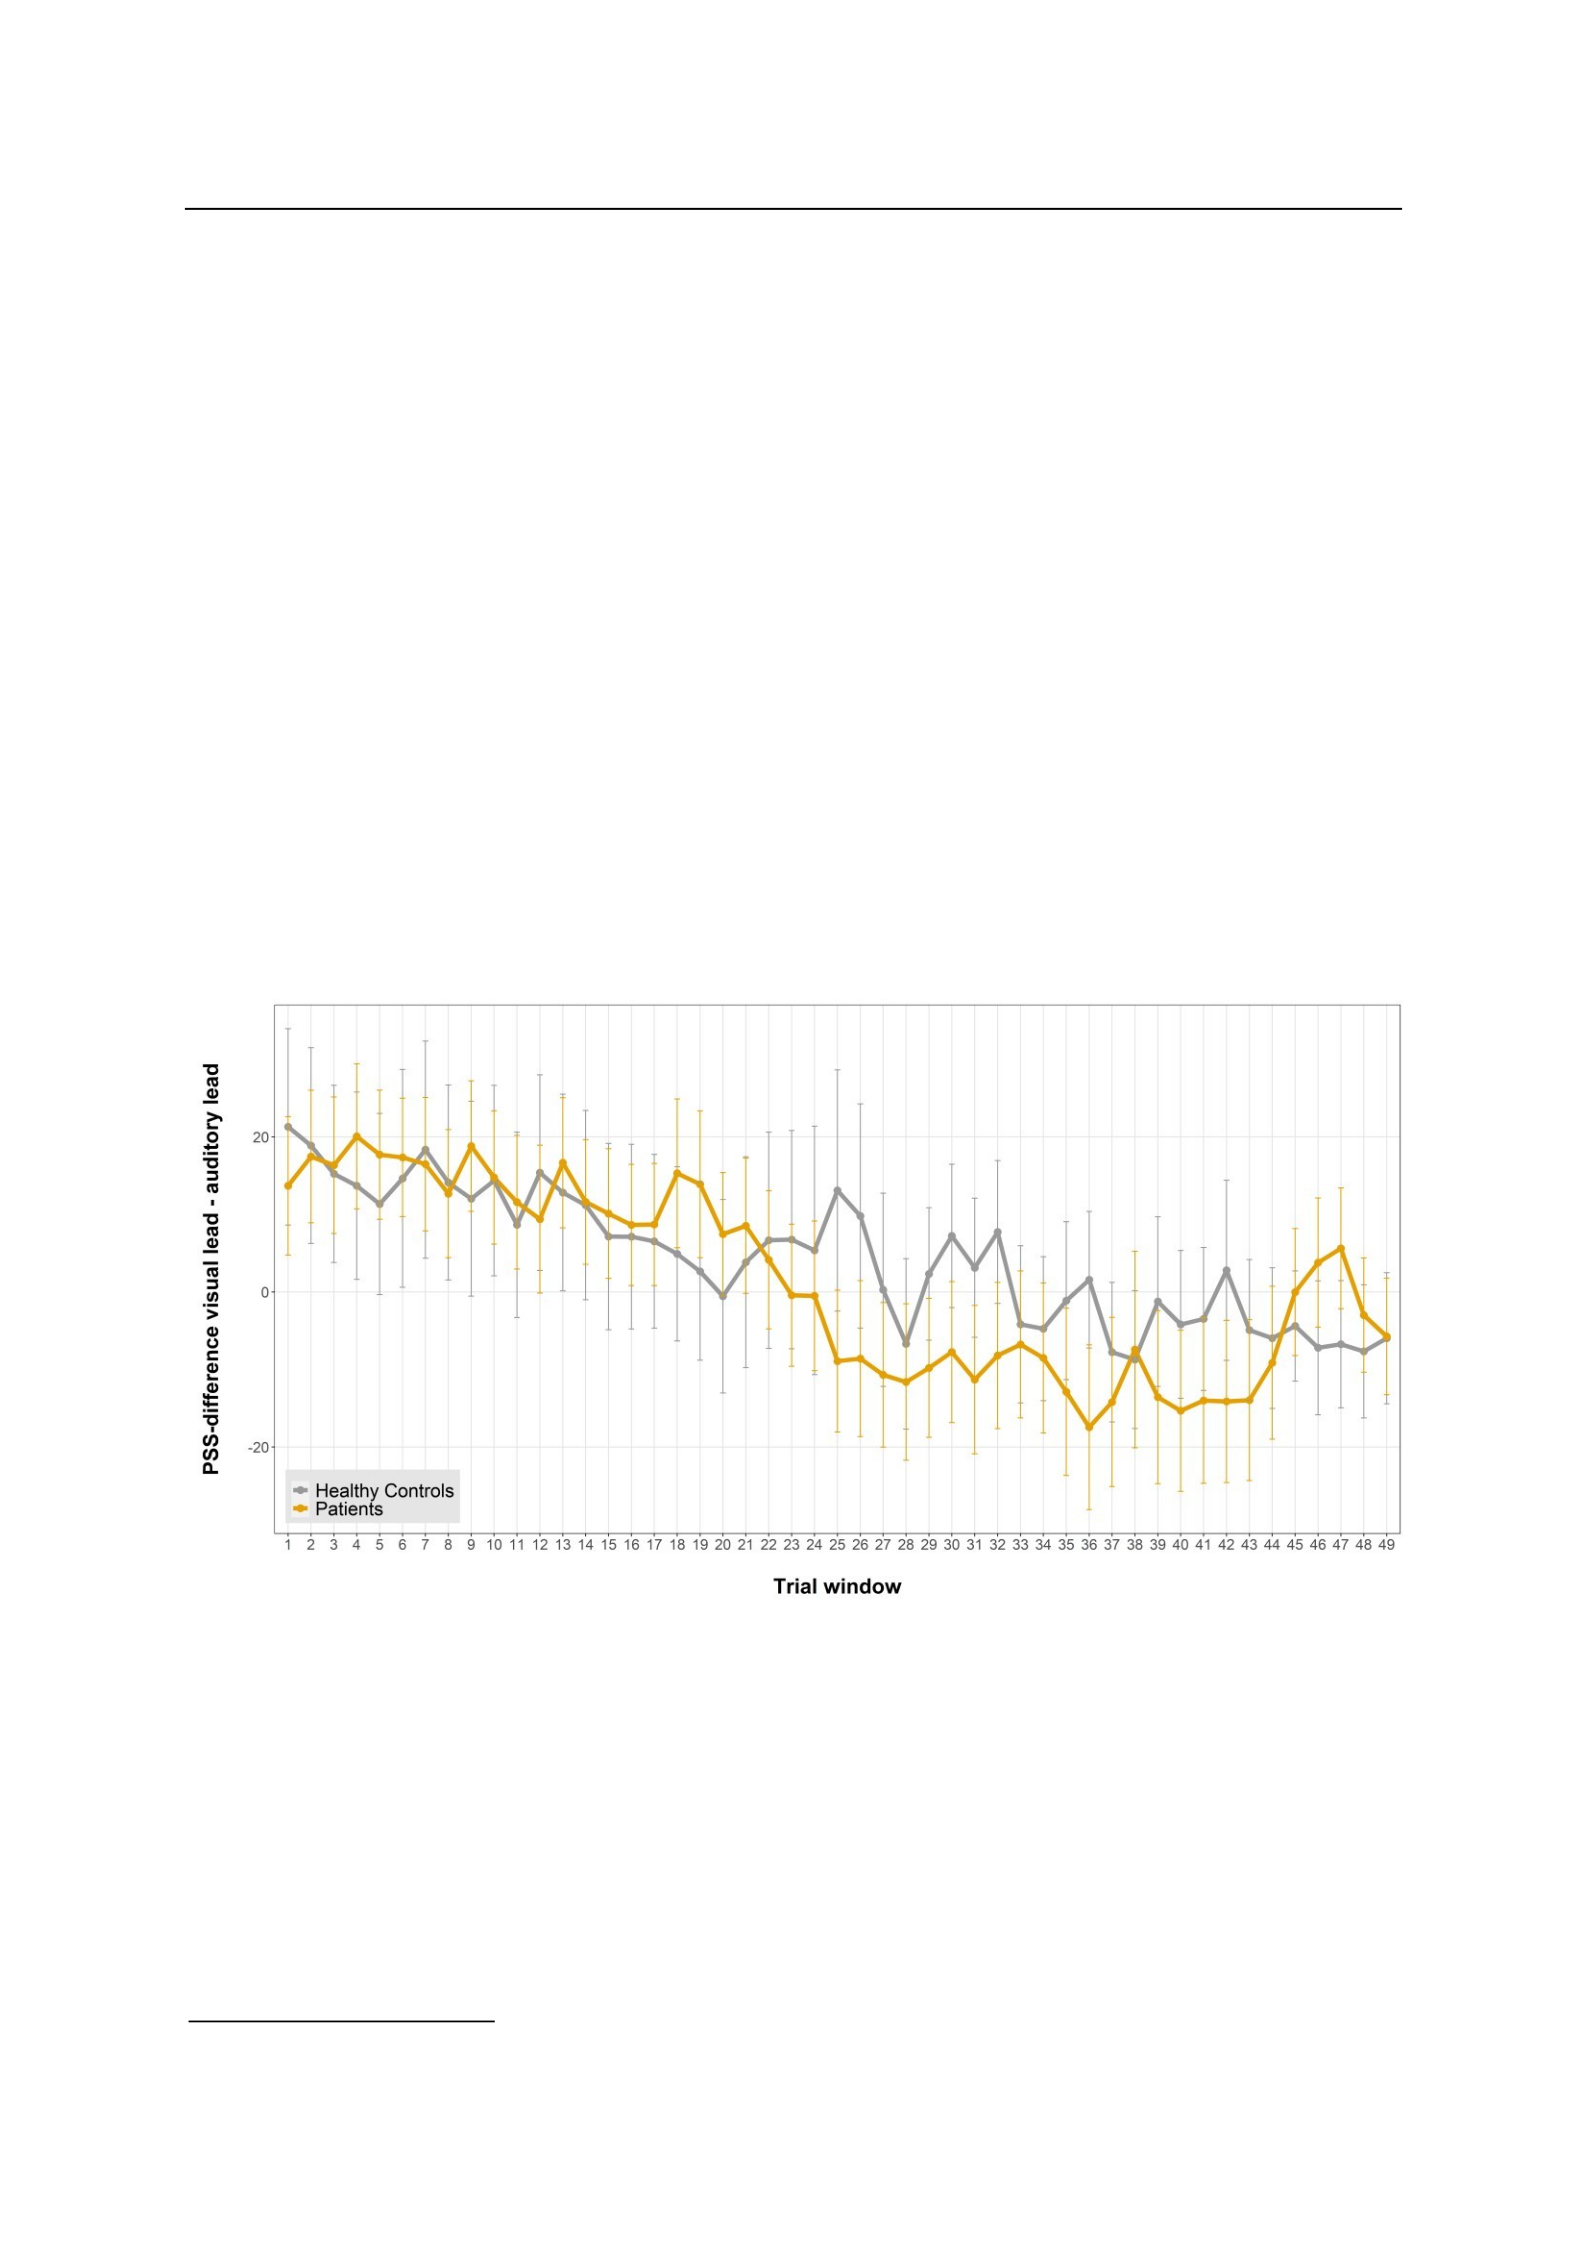
81
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
adapted test trials, i.e. the cumulative recalibration effect, in moving trial windows (i.e. 1-50,
2-51, and so on), all uncorrected p > .05, all FDR-corrected p = .984, all BF10 < 1 (see Figure 6
for the time course of the cumulative temporal recalibration effect for both groups). Further,
one-sample t-Tests against zero per group and trial window revealed no significant difference
to zero in any trial window for healthy controls, all uncorrected p > .05, all FDR-corrected p =
.906, all BF10 < 1. Before FDR-correction, patients showed a PSS-difference different from
zero in trial window 4, uncorrected p = .042, BF10 = 1.47, trial window 5, uncorrected p
= .044, BF10 = 1.42, trial window 6, uncorrected p = .032, BF10 = 1.82, and trial window 9,
uncorrected p = .034, BF10 = 1.71, which did not survive FDR-correction, all FDR-corrected p
= .464. All other comparisons were not statistically different from zero, all uncorrected p
> .05, all FDR-corrected p ≥ .464, all BF10 < 15.
Figure 6
Time Course of the Cumulative Recalibration Effect per Group
Notes. nPAT = 25; nHC = 27. Depicted is the PSS-difference between visual lead adapted minus auditory lead
adapted test trials. The respective PSS was estimated by means of the mean of a Gaussian fit over the respective
test trials in moving trial windows of 50 trials each, i.e. trials 1-50, 2-51 etc. p-values for each comparison are
FDR-corrected. Error bars denote ±1 standard error of the mean.
Time Course of Immediate Recalibration. There were no statistically significant
differences between groups in the PSS-difference between test trials preceded by a visual first
vs. auditory first test trials, i.e. the immediate recalibration effect, in moving trials windows,
5 With the exception of trial window 13, which was not significant in the frequentist analysis, uncorrected p
= .058, FDR-corrected p = .464, BF10 = 1.13.
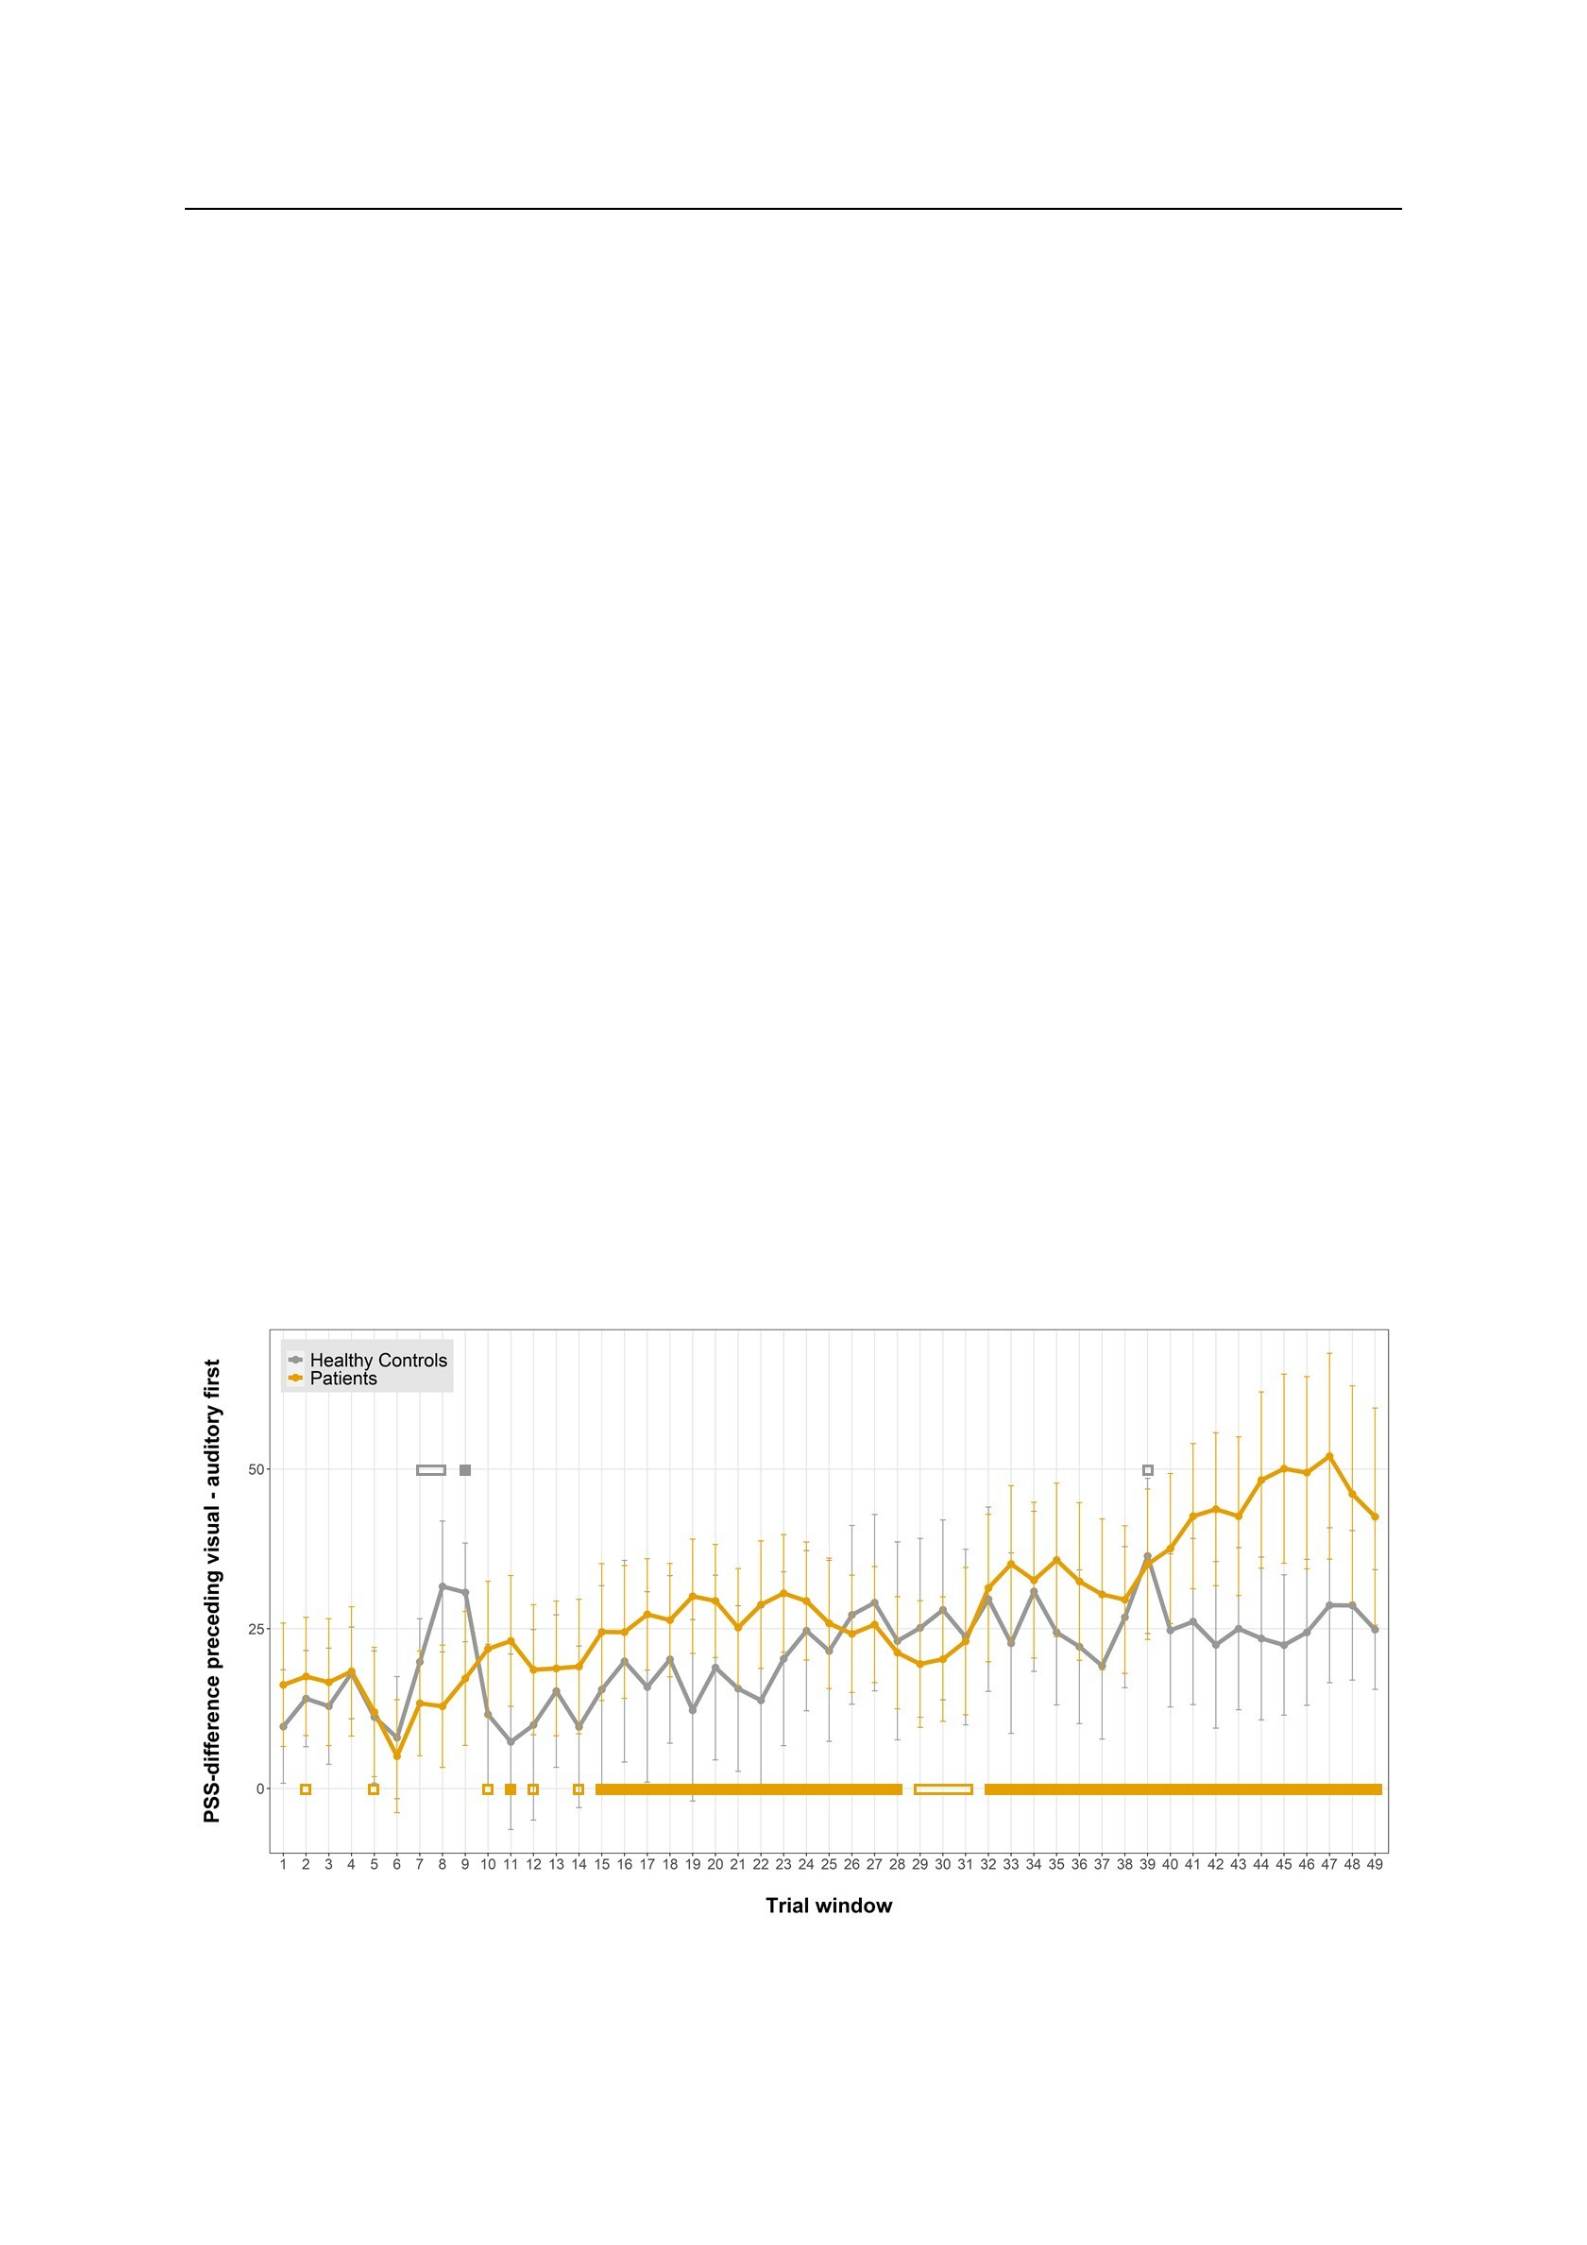
82
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
all uncorrected p > .05, all FDR-corrected p = .985, all BF10 < 1. (see Figure 7 for the time
course of the immediate temporal recalibration effect for both groups). For healthy controls,
the PSS-difference was significantly different from zero in trial window 9, t(26) = 3.97,
uncorrected p = < .001, FDR-corrected p = .025, BF10 = 62.33. Before, FDR-correction, the
PSS-difference was also significantly different from zero in trial windows 4, 7, 8, 27, 34, 35,
38, 39, 40, 46, 47, 48, 49, i.e. in some earlier but mostly middle to late trial windows, all
uncorrected p < .05. Out of these, only trial windows 7, 8, and 39 showed a non-significant
trend for a difference to zero after FDR-correction, all three FDR-corrected p = .086, all 6 <
BF10 < 10; the rest did not survive FDR-correction, all FDR-corrected p > .1, all 1 < BF10 < 4.
All other comparisons were not significant, all uncorrected p > .05, all FDR-corrected p > .1,
all BF10 < 1. For patients, the PSS-difference was significantly different from zero in trial
windows 11, 15-28, 32-49, i.e. in some earlier but mostly middle and late trial windows, all
uncorrected p < .05, all FDR-corrected p < .05, all 1 < BF10 < 36. Trial windows 2, 4, 10,
12 ,14, 29, 30 and 31 showed a non-significant trend for a difference to zero after
FDRcorrection, all FDR-corrected p <.1, all 0.5 < BF10 < 1.5. All other comparisons did not
survive FDR-correction, all FDR-corrected p > .1, all BF10 < 1.
Figure 7
Time Course of the Immediate Recalibration Effect per Group
Notes. nPAT = 25; nHC = 27. Depicted is the PSS-difference between test trials preceded by a visual first minus by
an auditory first test trial. The respective PSS was estimated by means of the mean of a Gaussian fit over the
respective test trials in moving trial windows of 50 trials each, i.e. trials 1-50, 2-51 etc. Filled rectangles denote a
significant difference from zero for the respective trial window per group, p < .05; hollow rectangles denote a

83
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
non-significant trend for a difference from zero, p < .1. p-values for each comparison are FDR-corrected. Error
bars denote ±1 standard error of the mean.
3.1.6 Correlations of Experimental Data
There were no significant Spearman rank correlations between the general TBW, the
cumulative recalibration effect (defined as the PSS-difference between the first 50 visual lead
minus auditory lead adapted test trials) and the immediate recalibration effect (defined as the
PSS-difference between test trials preceded by a visual first minus auditory first test trial), all
ρ < .3, all p > .05, all BF10 < 1 (see Table 4 for Spearman rank coefficients ρ over all
participants. Exploratory Spearman rank coefficients ρ split by group can be found in Table
C.1 and Table C.2 in Appendix C).
Table 4
Spearman Rank Correlation Coefficients ρ for Associations Between Experimental Data and
Questionnaire Scores over all Participants
1. 2. 3. 4. 5. 6. 7. 8.
1. TBW
2. Cumulative
Recalibration
.03
3. Immediate
Recalibration
.12 .04
4. CAPS -.08 .08 .07
5. LSHS-E -.12 .03 -.04 .87***
6. PCL -.05 .06 .14 .75*** .70***
7. Pass. Exp .01 -.11 -.01 .79*** .78*** .68***
8. BCSS n.S. -.16 -.02 .09 .66*** .66*** .58*** .56***
9. BCSS n.O. -.19 -.12 .13 .64*** .63*** .61*** .55*** .70***
Notes. N = 52. Spearman rank correlation coefficients ρ > .3 are marked in bold. p-values are
Bonferronicorrected. TBW = temporal binding window, defined as the bandwidth of the Gaussian fit over all test
trials; Cumulative Recalibration = cumulative recalibration effect, defined as the difference in mean of the
Gaussian fits, i.e. PSS, over the first 50 visual lead vs. auditory lead adapted test trials; Immediate Recalibration
= immediate recalibration effect, defined as the difference in mean of the Gaussian fits, i.e. PSS, over test trials
preceded by a visual first vs. auditory first test trial; CAPS = Cardiff Anomalous Perception Scale, total score;

84
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
LSHS-E = Launey-Slade Hallucination Scale-Extended, total score; PCL = Paranoia Checklist, total score; Pass.
Exp. = total score in passivity experiences items; BCSS n.S. = Brief Core Schema Scales, negative self subscale;
BCSS n.O. = Brief Core Schema Scales, negative other subscale.
* p < .05, ** p < .01, *** p < .001
3.2 Control Variables and Questionnaire Data
3.2.1 Control Tests for Attention, Processing Speed, and Vigilance
TMT. Groups differed significantly in completion time (in seconds) of the TMT-A
version, with patients (M = 32.79, SD = 13.21) requiring more time to complete the test
compared to healthy controls (M = 23.12, SD = 8.90), t(41.6) = 3.07, p = .004, Cohen’s d =
0.87, BF10 = 12.49. Further, patients (M = 78.12, SD = 30.34) showed higher completion times
in the TMT-B version compared to healthy controls (M = 61.03, SD = 26.24), t(47.65) =
2.16, p = .036, Cohen’s d = 0.6, BF10 = 1.88.
CPT-IP.6 A 2 (Group) * 3 (Digit Condition) mixed ANOVA on CPT-IP d’ scores
revealed a significant main effect of Group, F(1, 50) = 9.03, p = .004, η2p = 0.15, BFincl = 6.45,
indicating that patients (M = 2.84, SD = 0.83) showed overall lower d’ scores compared to
healthy controls (M = 3.46, SD = 0.6). There was a highly significant main effect of Digit
Condition, F(1.67, 83.48) = 129.57, p < .001, η2p = 0.72, BFincl > 1000. Bonferroni-corrected
post-hoc comparisons revealed that d’ scores were significantly larger in the 2-digit (M = 3.57,
SD = 0.65) compared to the 3-digit (M = 2.96, SD = 0.91), t(51) = 6.86, p < .001, and the 4-
digit condition (M = 1.85, SD = 1.04), t(51) = 13.41, p < .001, and larger in the 3-digit
compared to the 4-digit condition, t(51) = 10.81, p < .001. There was no Group * Digit
Condition interaction, F(1.67, 83.48) = 0.53, p = .557, η2p = 0.01, BFincl = 0.63.
Associations Between Experimental Data and Control Variables.
Bonferronicorrected Spearman rank correlations revealed significant associations between the
general
TBW and both the TMT-B version completion time, ρ = .40, p = .027, BF10 = 2.91, and the
CPT overall d’ score, ρ = -.52, p < .001, BF10 = 24.97. There were no other significant
associations between control tests and experimental data, all p > .05, all BF10 < 17 (see Table
C.3 in Appendix C for Spearman rank correlation coefficients ρ).
6 One patient did not complete the CPT-IP due to fatigue at the end of both sessions. Their CPT d’ scores were
replaced by the respective group mean to not lose the subject for further analysis.
7 With the exception of TBW ~ TMT-A completion time, which was not significant in the frequentist analysis:
Bonferroni-corrected p = .216, BF10 = 1.71

85
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
3.2.2 Questionnaires
CAPS. Groups differed in CAPS scores, with patients (M = 11.6, SD = 5.8) reporting a
significantly higher number of anomalous perceptual experiences compared to healthy
controls (M = 1.4, SD = 2.0), t(29.21) = 8.4, p < .001, Cohen’s d = 2.41, BF10 > 1000.
LSHS. LSHS scores differed significantly between groups, with patients (M = 24.3,
SD = 11.9) showing a higher occurrence of hallucinatory events compared to healthy controls
(M = 3.2, SD = 4.1), t(29.37) = 8.44, p < .001, Cohen’s d = 2.41, BF10 > 1000.
PCL. Groups differed significantly in PCL scores, indicating significantly higher
levels of paranoia in patients (M = 94.2, SD = 52.3) compared to healthy controls (M = 26.0,
SD = 26.2), t(34.72) = 5.88, p <. 001, Cohen’s d = 1.67, BF10 > 1000.
Passivity Experiences. Patients (M = 7, SD = 4.5) reported a significantly higher
frequency of passivity experiences compared to healthy controls (M = 0.1, SD = 0.5), t(24.45)
= 7.55, p < .001, Cohen’s d = 2.18, BF10 > 1000.
BCSS. Patients (M = 6.6, SD = 4.5) showed a significantly higher level of negative
schemata towards the self compared to healthy controls (M = 2, SD = 2.5), t(36.68) = 4.5, p
< .001, Cohen’s d = 1.28, BF10 = 653.69. Further, patients (M = 9.8, SD = 5.6) reported a
significantly higher level of negative schemata towards others compared to healthy controls
(M = 3.5, SD = 3.8), t(42.09) = 4.77, p < .001, Cohen’s d = 1.34, BF10 > 1000.
Correlations Between Questionnaire Scores. CAPS, LSHS, PCL, passivity
experiences and both BCSS negative subscales all showed highly significant, strong positive
Spearman rank correlations with each other, all ρ > .5, all Bonferroni-corrected p < .001, all
BF10 > 308 (see Table 4 for Spearman rank coefficients ρ. Exploratory Spearman rank
coefficients ρ split by group can be found in Table C.1 and Table C.2 in Appendix C).
3.3 Correlations Between Experimental Data and Questionnaire Scores
There was no significant Spearman rank correlation between the general TBW, the
cumulative recalibration effect, the immediate recalibration effect and questionnaires scores,
all ρ < .3, all Bonferroni-corrected p > .05, all BF10 < 1 (see Table 4 for Spearman rank
coefficients ρ. Exploratory Spearman rank coefficients ρ split by group can be found in Table
C.1 and Table C.2 in Appendix C).
8 The majority of BF10 for correlations between questionnaire scores was > 1000, with following exceptions:
LSHS ~ BCSS negative other BF10 = 992.48; PCL ~ BCSS negative self BF10 = 288.32; passivity experiences ~
BCSS negative self BF10 = 30.95; passivity experiences ~ BCSS negative other BF10 = 136.02.

86
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
4 Discussion
In this study, we investigated temporal MSI and crossmodal temporal recalibration in
psychosis. While considerable work on temporal MSI in patients with the diagnosis of a
psychotic disorder has been published (Noel et al., 2018; Zhou et al., 2018; for a review and
meta-analysis, see Zhou, Lai, et al., 2022; Zopf et al., 2021), to our knowledge no published
study investigated cumulative and immediate crossmodal temporal recalibration in psychosis.
Only one recent study provided initial findings on immediate temporal recalibration in
extraordinarily rare EOS (Zhou, Cui, et al., 2022), but generalizability to adult-onset
psychosis might be limited. Based on previous evidence reporting deficits in time perception
and temporal processing in psychosis (Amadeo et al., 2022; Ciullo et al., 2016; Thoenes &
Oberfeld, 2017; Wallace et al., 2020; Wallace & Stevenson, 2014; Zhou et al., 2018) as well as
prior findings of impaired crossmodal temporal recalibration in ASD (Noel, De Niear, et al.,
2017; Turi et al., 2016; Zhou, Cui, et al., 2022), a neurodevelopmental disorder sharing
several aspects with psychosis including an increased TBW during temporal MSI (Zhou et al.,
2018), we expected to observe altered crossmodal temporal recalibration in psychosis.
Patients with the diagnosis of a psychotic disorder and healthy controls concluded
several phases of a SJ task with simple AV stimuli. Before each SJ phase, the same AV stimuli
were presented with a fixed SOA, half visual lead and half auditory lead (paradigm adopted
from Van der Burg et al., 2015). Further, all subjects completed neuropsychological tests for
processing speed, attention, and vigilance as well as questionnaires for psychotic symptoms
and negative schemata. We analyzed the SJ data of patients and healthy controls and
compared the TBW over all SJ trials, the PSS-difference between visual lead adapted vs.
auditory lead adapted SJ trials, i.e. the cumulative recalibration effect, and the PSS-difference
in SJ trials immediately preceded by a visual first vs. auditory first SJ trial, i.e. the immediate
recalibration effect, between both groups.
Patients and healthy controls did not differ in the TBW over all trials, the PSSdifference
between visual lead adapted vs. auditory lead adapted SJ trials, and the PSSdifference in SJ
trials with a preceding visual vs. auditory first SJ trial. This indicates that both groups showed
comparable temporal MSI, cumulative temporal recalibration, and immediate temporal
recalibration. In the following, these results will be discussed in more detail with respect to
our hypotheses and previous findings on temporal multisensory processing in psychosis.

87
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
4.1 Hypothesis 1: Psychosis and the TBW
Our first aim was to replicate previous findings on an increased TBW in psychosis
(Noel et al., 2018; Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021). Contrary to
our expectation, we did not observe a difference in the bandwidth of the Gaussian fit over all
SJ test trials between patients and healthy controls. While the mean bandwidth was
descriptively slightly larger in patients than in controls, i.e. pointed in the expected direction,
this difference was not significant with a small effect size. Further, our additional Bayesian
analysis revealed a BF < .333, reflecting moderate evidence for the null hypothesis. This
indicates that the general TBW did not differ between both groups, reflecting a similar
distribution of positive SJ responses between patients and healthy controls. Thus, our sample
of patients with the diagnosis of a psychotic disorder did not show an enlarged TBW
compared to controls.
Our findings are consistent with a study by de Boer-Schellekens et al. (2014), who
observed impaired temporal acuity in patients compared to controls during a TOJ task in a
visual only condition, but comparable TOJ performance between both groups when two
sounds were presented in addition to the visual stimuli. This indicated that additional
presentation of auditory cues ameliorated deficits in visual temporal processing, reflecting
intact AV temporal integration (de Boer-Schellekens et al., 2014) and suggesting potential
compensatory effects of crossmodal gains in psychosis. This is consistent with previous
studies reporting intact multisensory facilitation in psychosis using AV target detection
(Wynn et al., 2014) or AV far-near judgement paradigms (Stephen et al., 2013; Stone et al.,
2011), suggesting a potential influence of task type or task demands on crossmodal gains in
psychosis.
However, our findings are inconsistent with the majority of previous studies on
multisensory temporal processing in psychosis. An enlarged multisensory TBW has repeatedly
been observed in psychosis and it has been discussed that the enlargement of the
TBW might be more pronounced in speech compared to simple AV stimuli (Noel et al., 2018;
Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021). Several other studies investigated
the TBW in visual, i.e. unimodal stimuli. The majority of those reported an enlarged visual
TBW in psychosis (for a review and meta-analysis, see Zhou et al., 2018), with only one study
failing to observe impaired visual temporal processing (Grimsen et al., 2013). Crucially,
impairments in AV temporal processing were observed to go beyond unisensory processing

88
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
deficits (Stevenson, Park, et al., 2017; Zhou, Lai, et al., 2022), highlighting the importance of
investigating multisensory temporal processing in psychosis. In sum, while previous evidence
indicated an impairment in visual and AV asynchrony detection in psychosis reflected by an
enlarged TBW (Noel et al., 2018; Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021),
our findings are in contrast to previous work.
An enlarged multisensory TBW has been discussed as a potential core deficit in
psychosis (Amadeo et al., 2022). As mentioned above (see 1.3 Temporal Multisensory
Processing in Psychosis), an enlarged multisensory TBW might lead to erroneous integration
of stimuli originating from distinct sources, facilitating anomalous and confusing percepts and
potentially leading to psychotic symptoms (Zhou et al., 2018). A meta-analysis by Zhou et al.
(2018) on the uni- and multisensory TBW in psychosis reported a large effect size of the
enlarged TBW, i.e. a Hedge’s g > 0.8, in both unimodal visual and AV stimuli. However, only
two out of the above mentioned multisensory studies could be included in the metaanalysis by
Zhou et al. (2018). This implies that more studies and a more current metaanalytic approach
are needed to obtain robust findings on a potentially large effect size of an enlarged
multisensory TBW in psychosis and to gather experimental support for the hypothesis on a
potential role of impaired temporal MSI in the development of psychosis (Amadeo et al.,
2022; Zhou et al., 2018).
Importantly, the designs of previous studies on AV temporal processing in patients with
the diagnosis of a psychotic disorder varied, including SJ (Foucher et al., 2007; Noel et al.,
2018; Stevenson, Park, et al., 2017; Zhou, Lai, et al., 2022), TOJ (de Boer-Schellekens et al.,
2014), double-flash illusion (Haß et al., 2017), stream-bounce illusion (Zvyagintsev et al.,
2017) as well as McGurk paradigms (B. Martin et al., 2013) and – moreover – some
investigated simple and others speech stimuli. Taken together, these differences in study
designs might limit comparability between studies and it could be argued that different
complexity of stimulus material and task might partially account for diverging results such as
the findings from de Boer-Schellekens et al. (2014) and our study.
It is important to note that the general TBW, reflected by the mean bandwidth over all
SJ trials, showed a high variability in both our patient and control groups, minimizing the
possibility to statistically detect small differences. Crucially, this variability of the TBW was
comparable between our patient and control samples, whereas previous studies reported a
larger variability in patients with the diagnosis of a psychotic disorder compared to healthy

89
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
controls (de Boer-Schellekens et al., 2014; Foucher et al., 2007; B. Martin et al., 2013; Noel et
al., 2018; Stevenson, Park, et al., 2017; Zhou, Lai, et al., 2022). This further suggests that AV
temporal processing was similar in our patient and control samples in contrast to previous
studies.
It is possible that we failed to observe an enlarged TBW in simple AV stimuli in
psychosis, since the TBW enlargement in psychosis is discussed to be larger in speech
compared to simple stimuli (Zhou et al., 2018). Previous evidence suggested that - beyond the
temporal domain - MSI deficits might be pronounced in psychosis in socially relevant
information, i.e. stimuli with linguistic or emotional content, compared to simple cues (Tseng
et al., 2015). However, an enlarged TBW in psychosis has repeatedly been observed using
simple AV stimuli (Foucher et al., 2007; Haß et al., 2017; Stevenson, Park, et al., 2017; Zhou,
Lai, et al., 2022; Zvyagintsev et al., 2017), so it could be argued the findings in our patient
sample might due to methodological differences or specific for our sample. Nevertheless,
comparing our findings in our patient sample of intact temporal MSI with simple AV stimuli
to an additional condition with AV speech stimuli could be informative for further hypothesis
generation regarding factors, which potentially influence temporal MSI in simple stimuli vs.
speech in psychosis.
Temporal processing impairments in psychosis have been observed both in SJ and TOJ
tasks (Noel et al., 2018; Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021). However,
Capa et al. (2014) reported that deficient temporal processing in patients with the diagnosis of
a psychotic disorder was pronounced in a visual TOJ compared to a visual SJ tasks,
suggesting a specific impairment in temporal ordering compared to asynchrony detection
(Capa et al., 2014). It is possible that we failed to observe group differences in AV temporal
processing since we administered a SJ rather than a TOJ task. However, most of previous
studies on multisensory temporal processing in psychosis administered SJ tasks, indicating a
deficit in multisensory asynchrony detection. Nevertheless, it might be possible that we would
have observed significant group differences using a multisensory TOJ task. It has been
discussed that TOJ tasks require additional cognitive resources compared to SJ tasks (García-
Pérez & Alcalá-Quintana, 2012), which might be deficient in psychosis. Patients with the
diagnosis of a psychotic have been observed to perceive stimuli individually rather than in
sequence, i.e. fail to structure events relative to each other in time. It has been discussed that
this impairment might root in a deficit in predicting future events while the present event is

90
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
still in focus, leading to a disintegration of temporal information processing in psychosis
(Amadeo et al., 2022). Thus, it might be possible that our patient sample might have shown
impaired performance during a TOJ task, while the cognitive resources were intact enough for
typical SJ performance. Future research should address this and directly compare
multisensory SJ and TOJ tasks to investigate temporal MSI and crossmodal temporal
recalibration (see 4.2 Hypothesis 2: Psychosis and Crossmodal Temporal Recalibration) in
psychosis and thus to study if specific impairments in temporal ordering of events might
influence both aspects of multisensory temporal processing in psychosis.
We conclude that further research is needed to disentangle possible reasons for the
contradictory findings of de Boer-Schellekens et al. (2014) and our study. Future studies
should specifically examine where the potential effects of impaired temporal MSI in psychosis
might lie. Possible candidate factors might be found in e.g. stimulus and task complexity, such
as specific impairments in multisensory speech processing (Zhou et al., 2018) or temporal
ordering of sensory events (Capa et al., 2014). Further, investigating temporal MSI in patient
samples with larger variability of cognitive impairments or symptom severity might be
beneficial to elucidate the potential effects of cognitive abilities and symptom load, which has
been suggested in previous (Foucher et al., 2007; Stevenson, Park, et al., 2017; Zhou, Lai, et
al., 2022). Moreover, by directly comparing temporal MSI in samples on different stages of
the psychosis spectrum such as subjects with psychosis proneness, first-episode patients,
patients in an acute psychotic episode or patients with chronic psychosis, future studies might
succeed in gaining further support for theoretical accounts suggesting a role of an enlarged
multisensory TBW for the development of psychosis (Amadeo et al., 2022; Zhou et al., 2018).
4.2 Hypothesis 2: Psychosis and Crossmodal Temporal Recalibration
4.2.1 Discussion and Comparison to Previous Evidence
Our second aim was to provide first experimental evidence on cumulative and
immediate crossmodal temporal recalibration in psychosis. We expected to observe altered
crossmodal recalibration in our patient sample, since psychosis has been reported to be
associated with marked deficits in time perception and temporal processing (Amadeo et al.,
2022; Ciullo et al., 2016; Thoenes & Oberfeld, 2017; Wallace et al., 2020; Wallace &
Stevenson, 2014; Zhou et al., 2018). Further, previous evidence suggested deficient
crossmodal temporal recalibration in ASD (Noel, De Niear, et al., 2017; Stevenson, Toulmin,
et al., 2017; Turi et al., 2016; Zhou, Cui, et al., 2022), a neurodevelopmental disorder sharing

91
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
deficits in temporal processing with psychosis (Zhou et al., 2018). We regarded these findings
as hints for possibly deficient crossmodal temporal recalibration in psychosis.
We overall successfully replicated the findings of Van der Burg et al. (2015). In the
first 50 SJ trials, the PSS in visual lead adapted SJ trials was shifted towards the visual lead
adapted SOAs compared to the auditory lead adapted SJ trials. This PSS shift in direction of
the respective SOA during preceding adaptation phases reflects the cumulative recalibration
effect first reported by Fujisaki et al. (2004) and Vroomen et al. (2004), which has been
successfully replicated since (e.g. Di Luca et al., 2009; Stevenson, Toulmin, et al., 2017; Uno
& Yokosawa, 2022; Van der Burg et al., 2015). Further, the PSS in SJ trials with an
immediately preceding visual first SJ trial was significantly shifted towards the previous
trial’s visual first SOA compared to SJ trials preceded by an auditory first SJ trial. This PSS
shift in direction of the immediately preceding SOA reflects the immediate temporal
recalibration effect first reported by Van der Burg et al. (2013) and indicates rapid
recalibration processes depending on the immediate stimulus history.
However, contrary to our expectation the effect of adaptation, i.e. if SJ trials were
visual lead vs. auditory lead adapted, on the PSS over the first 50 SJ trials did not differ
between groups, as reflected by a lack of a significant interaction. This indicates that the
cumulative recalibration effect in the first 50 SJ trials following consistent AV adaptation did
not differ between patients and healthy controls. Thus, our patient sample showed intact
cumulative temporal recalibration in the first 50 SJ trials directly after prolonged adaptation,
i.e. in the time frame in which the cumulative temporal recalibration effect has been observed
to be largest (Van der Burg et al., 2015).
To our knowledge, our study is the first to investigate cumulative temporal
recalibration in psychosis. We therefore compare our results to one previous study by
Stevenson, Toulmin et al. (2017) on cumulative temporal recalibration and autistic traits.
Healthy participants performed a SJ task with preceding visual lead vs. auditory lead
adaptation, analogue to our design. The authors observed a significant association between a
decrease in the cumulative recalibration effect and autistic traits, suggesting a link between
symptoms of ASD and impaired cumulative temporal recalibration (Stevenson, Toulmin, et
al., 2017). Given the scarcity of evidence regarding cumulative temporal recalibration in
neurodevelopmental disorders such as psychosis and ASD, interpretations and conclusions
should be drawn with caution. It is possible that future studies might confirm that ASD is

92
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
associated with a deficit in cumulative temporal recalibration, i.e. an impaired ability to
perceptually adjust to consistent asynchronies. Further, it also is possible that psychosis is not
or weaker associated with impaired cumulative recalibration compared to ASD, as our
findings might suggest. To date, further research on cumulative recalibration both in psychosis
and ASD is urgently needed to confirm or reject this speculation of potentially different
impairments in cumulative temporal recalibration in psychosis and ASD.
Our results on the immediate recalibration effect also contrast our expectations: the
effect of modality order on the immediately preceding SJ trial on the PSS over all test trials
did not differ between groups, as reflected by a lack of a significant interaction. This indicates
that the immediate recalibration effect did not differ between patients and healthy controls.
Thus, our findings suggest that patients showed intact immediate temporal recalibration over
all SJ trials, i.e. recalibrated their SJ responses depending on the immediate stimulus history
similarly as healthy controls.
Our results of an unimpaired immediate temporal recalibration effect are consistent
with initial results of intact immediate recalibration in children and adolescents with the
diagnosis of EOS (Zhou, Cui, et al., 2022). Crucially, the transferability of the findings of
Zhou, Cui et al. (2022) to adult patients with the diagnosis psychosis might be limited due to
marked differences in premorbid cognitive impairment as well as symptom severity between
early- and adult-onset psychosis (Vyas et al., 2011) and potential age-related confounds in
temporal recalibration processes (Noel et al., 2016; Zhou et al., 2020) in the study of Zhou,
Cui, et al. (2022). Nonetheless, further support might be found in an earlier study by Zhou et
al. (2020). In their study, the authors investigated immediate temporal recalibration during a
SJ task in healthy participants and expected associations between a reduction of the immediate
recalibration effect and increased schizotypal and autistic traits. However, Zhou et al. (2020)
failed to observe the expected correlation to schizotypal traits, suggesting that there might be
no direct link between subclinical psychotic symptoms and immediate AV temporal
recalibration. It could be argued that this finding of Zhou et al. (2020) matches our results of
unimpaired immediate recalibration in our patient sample. In sum, previous findings in
healthy individuals with schizotypal traits and in minors with the diagnosis of early-onset
psychosis could - along with our initial findings in adult patients with the diagnosis of a
psychotic disorder - indicate that psychosis might not be associated with impaired immediate

93
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
recalibration, suggesting that patients with the diagnosis of a psychotic disorder might be able
to rapidly recalibrate to AV asynchronies in the immediate stimulus history.
However, our findings in psychosis are in contrast with studies on immediate temporal
recalibration in ASD. Turi et al. (2016) investigated immediate temporal recalibration in
adults with the diagnosis of an ASD and observed that patients hardly recalibrated their SJ
responses to AV asynchronies in the immediate stimulus history compared to controls. This
reduction in immediate temporal recalibration in ASD was replicated in children and
adolescents with the diagnosis of an ASD by Noel, De Niear et al. (2017) and Zhou, Cui, et al.
(2022), suggesting a deficit to rapidly recalibrate to preceding AV asynchronies in the
developmental trajectory of ASD. Interestingly, while Noel, De Niear et al. (2017) observed
an intact immediate recalibration effect in speech and deficits in simple and complex non-
speech stimuli, Zhou, Cui, et al. (2022) observed the opposite pattern, i.e. deficits in speech
but not in simple stimuli. Thus, the findings of Zhou, Cui. et al. (2022) matched the pattern of
previous studies on pronounced temporal processing deficits in speech in ASD (e.g. Stevenson
et al., 2014), while the study of Noel, De Niear et al. (2017) contrasted them. As mentioned
earlier, deficits in multisensory processing in psychosis have been discussed to be pronounced
in speech compared to simple stimuli (Tseng et al., 2015; Zhou et al., 2018). While our study
provides initial results suggesting intact immediate recalibration in psychosis, it is possible
that a different pattern might emerge when investigating immediate recalibration in psychosis
using speech compared to simple stimuli.
In sum, our study provides first evidence on cumulative and immediate crossmodal
temporal recalibration. While our results suggest intact crossmodal recalibration in patients
with the diagnosis of a psychotic disorder, future studies should aim to replicate our findings
with larger samples to investigate if our findings might be e.g. specific for our patient sample,
which potentially showed relatively spared temporal processing capabilities.
4.2.2 Deficits in Perceptual Prediction as an Underlying Mechanism
Stevenson, Toulmin et al. (2017) argued that a possible cumulative temporal
recalibration deficit in individuals with autistic traits might be rooted in perceptual inference
dysfunctions, which have been previously reported in ASD (for reviews, see Pellicano & Burr,
2012; Sinha et al., 2014). Stevenson, Toulmin et al. (2017) proposed that decreased
cumulative temporal recalibration to statistically regular AV asynchronies reflects an impaired
ability to weigh priors, i.e. mental representations or models of the environment acquired and

94
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
updated through experience, in relation to incoming sensory input during perceptual inference.
This might decrease the impact of repeatedly presented AV asynchronies on perception and
inhibit cumulative crossmodal recalibration (Stevenson, Toulmin, et al., 2017). Further, both
Noel, De Niear et al. (2017) and Zhou, Cui, et al. (2022) proposed an analogue argumentation
for impaired immediate temporal recalibration in ASD and argued that a deficit in weighing
perceptual priors and thus an overweighing of sensory input, i.e. the currently perceived AV
asynchrony, leads to insufficient recalibration processes to AV asynchronies in the immediate
stimulus history (Noel, De Niear, et al., 2017; Zhou, Cui, et al., 2022).
Importantly, dysfunctions in perceptual inference, as described by the predictive
coding framework, have also been reported in psychosis and it has been proposed that altered
weighing of priors and sensory input might be a core deficit in psychosis, potentially even
contributing to the development of psychotic symptoms (for reviews, see Heinz et al., 2019;
Sterzer et al., 2018). While ASD has been discussed to show specific impairments in weighing
of priors (Pellicano & Burr, 2012), psychosis might be associated with altered weighing of
both priors and sensory input (Sterzer et al., 2018). On the one hand, previous studies reported
impaired weighing of priors in psychosis (e.g. Schmack et al., 2013, 2015; Stuke et al., 2018),
leading to a weakened impact of prior knowledge on perception and volatile belief updating.
This incites the speculation that psychosis could be associated with decreased crossmodal
temporal recalibration, i.e. analogue to mechanisms in ASD as proposed by Noel, De Niear et
al. (2017), Stevenson, Toulmin, et al. (2017) and Zhou, Cui, et al. (2022). On the other hand,
some studies reported overweighing of priors in psychosis, shaping perception based on
overly fixed prior beliefs (e.g. Davies et al., 2018; Limongi et al., 2018; Powers et al., 2017;
Schmack et al., 2017; Teufel et al., 2015). This encourages the question, if overweighing of
priors in psychosis might be associated with an increased impact of statistically regular AV
asynchronies or asynchronies in the immediate stimulus history on recalibration processes,
potentially resulting in excessive crossmodal temporal recalibration. However, our findings do
not offer support for either hypothesis, with our patient sample showing intact cumulative and
immediate temporal recalibration.
Importantly, Noel et al. (2018) revealed potential differences between psychosis and
ASD regarding underlying inference mechanisms of altered multisensory temporal
processing. Using a causal inference modeling approach, Noel et al. (2018) showed that an
enlarged TBW might be rooted in changes in binding priors in ASD, whereas the enlarged

95
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
TBW in psychosis might be rather a consequence of changes in both binding priors and
sensory input. This suggested that although both disorders show comparable
phenomenological manifestations of altered temporal MSI, i.e. an enlarged TBW, the
underlying mechanism might be different (Noel et al., 2018). Thus, future studies on
perceptual inference mechanisms in both temporal MSI and crossmodal temporal recalibration
in psychosis and ASD might differentiate the underlying mechanisms in both disorders. This
could contribute to answering the question if psychosis and disorder might be differently
impaired in multisensory temporal processes, as our data on crossmodal temporal
recalibration in psychosis in contrast to previous findings in ASD might suggest.
Crucially, perceptual inference impairments as described by the predictive coding
account of psychosis are discussed to be influenced by a multitude of factors such as the
hierarchical level of inference processes or disorder progression status, implying a complex
framework for understanding psychosis in need of further research (Sterzer et al., 2018). This
suggests that more studies on crossmodal temporal recalibration in psychosis are needed,
targeting diverse cognitive hierarchical levels, e.g. by using differently complex stimuli, or
recruiting patients in various stages of disorder progression, such as first-episode psychosis,
chronic psychosis or patients in an acute vs. non-acute psychotic phase, and by this
investigating crossmodal temporal recalibration in psychosis and its potential relations to
dysfunctions in perceptual inference mechanisms.
4.2.3 Larger Bias Towards Visual Lead Asynchronies in Psychosis
In both the analyses for the cumulative and immediate recalibration effect, respectively,
a main effect of group indicated that the PSS differed between patients and healthy controls.
This reflected a shift towards visual leading SOAs in the patient compared to the healthy
control group. While a bias to perceive AV stimuli more often as synchronous in visual
leading compared to auditory leading stimuli has been reported in healthy participants
(Vroomen & Keetels, 2010), our findings suggest that this bias towards visual leading SOAs
might be larger in our patient sample compared to healthy controls. It could be argued that this
might indicate that the TBW in patients might have been not entirely similar compared to our
control group. It could be possible that we did not find TBW differences (see 4.1 Hypothesis
1: Psychosis and the TBW) because we did not differentiate between auditory and visual
leading stimuli but averaged over both. Potentially, the enlargement of the TBW in psychosis
might not be symmetrical, but might possibly be primarily driven by a larger bias towards

96
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
visual lead compared to auditory lead stimuli, i.e. a skewed TBW enlargement favoring visual
leading stimulus pairs. This might facilitate the perception of asynchronous AV stimuli as
synchronous, especially when the visual stimulus is first. To our knowledge however, no
published study so far has compared PSS biases in psychosis in visual vs.
auditory lead AV stimuli during SJ. This highlights the importance for future studies to not
only investigate the TBW on multisensory temporal processing in psychosis, but also possible
PSS shifts towards visual leading stimulus pairs.
4.2.4 Time Course of Cumulative and Immediate Recalibration
Additionally, we ran an exploratory analysis for the time course of both the cumulative
and the immediate recalibration effect and compared the time course of both effects between
groups as well as within each group against zero. There was no statistically significant
difference between patients and healthy controls in any trial window for neither effect,
indicating that the time course of both the cumulative and the immediate temporal
recalibration effect did not differ between groups.
Regarding the time course of cumulative recalibration, it descriptively seemed that the
cumulative recalibration effect for both groups was largest directly after prolonged adaptation
and decayed over time, which would be consistent with the findings of Van der Burg et al.
(2015). However, FDR-corrected comparisons against zero separately for both groups did not
reach statistical significance in any time window. It is likely that the large variability in the
cumulative recalibration effect per trial window (see Figure 6) within each group limited the
possibility of observing significant differences against zero within in each group.
For the time course of immediate recalibration, the effect seemed rather stable in the
control group, which would be consistent with the findings of Van der Burg et al. (2015), but
it descriptively seemed to increase over time in the patient group. FDR-corrected comparisons
against zero separately for healthy controls indicated (trends for) differences against zero in
two early and one later trial window. For the patient group, however, most of the trial
windows showed FDR-corrected (trends for) differences against zero, which were especially
observable in middle to late trial windows. This supported the descriptive impression of an
increase of the immediate recalibration effect over time in our patient sample.
Seen from a perceptual inference perspective, this impression of a potential increase of
the immediate recalibration effect in our patient sample allows the question, if psychosis

97
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
might be associated with specific changes in weighing prior knowledge and sensory input
over time during immediate recalibration. Dysfunctions in perceptual inference mechanisms,
as described by the predictive coding account, have been reported in psychosis (Sterzer et al.,
2018) and it has been discussed that psychosis proneness might be associated with a decreased
binding tendency, i.e. a decreased prior to integrate crossmodal stimuli (Odegaard & Shams,
2017). To our knowledge, however, the time course of perceptual inference mechanisms in
psychosis has been scarcely studied. It might be interesting to investigate if psychosis is
associated with altered learning mechanisms during perceptual inference, e.g. if patients
require more time, i.e. more stimulus exposure, to form or update priors or if weighing prior
knowledge and sensory input might differently change over time in psychosis. Support for
altered learning mechanism might be found in a study by Powers et al. (2017), who used a
modeling approach to investigate perceptual inference mechanisms in AV association learning
during AV stimulus detection. Powers et al. (2017) observed a decreased volatility parameter
during AV association learning, suggesting that perceptual priors in AV stimulus processing
might be resistant to updating in psychosis. Future studies should aim to investigate if this
resistance of perceptual prior updating in psychosis might be associated with altered time
courses of multisensory temporal processing.
In sum, our exploratory analysis of the time courses of crossmodal temporal
recalibration partly replicated the findings of Van der Burg et al. (2015), who reported a
decrease of the cumulative recalibration effect after adaptation phases but a rather stable
immediate recalibration effect. However, our data might give first hints for a potential
difference in time course of immediate temporal recalibration in psychosis. Future research
should specifically investigate the time courses of cumulative and immediate temporal
recalibration in psychosis and study if this is associated with changes over time in the
accumulation of prior knowledge or in weighing of priors and sensory input during inference
mechanisms.
4.2.5 A Theoretical Approach for Altered Temporal Recalibration as a Mechanism
Underlying Psychotic Symptoms
To our knowledge, only one review aimed to discuss a potential link between altered
temporal recalibration mechanisms and the development of psychotic symptoms. In their
review, Riemer (2018) argued that altered sensorimotor temporal recalibration might form a
potential basis for the emergence of delusions of control, i.e. the conviction that one’s own

98
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
actions are controlled by external forces (Sass & Parnas, 2003). In healthy subjects, it has
been discussed that the conscious intention of an action follows the perception of the action
itself (with the intention being unconscious up to that time point). The sense that the action
was self-caused is then inferred by internal temporal recalibration processes, which
subjectively contract the timings of the conscious intention and the sensory perception of the
action, leading to a temporal order of intention and action making sense to us (Haggard et al.,
2002; Wenke & Haggard, 2009). Riemer (2018) proposed that impaired temporal recalibration
of the perception of own actions and their conscious intention is a potential key mechanism
behind delusions of control in psychosis. They argue that a deficit in temporal shifting the
conscious intention before the perceived action results in a more veridical temporal perception
of the time structure of behavior and intention, which however is confusing and does not
make sense (Riemer, 2018). This might facilitate the feeling that the action was not self-
intended, leading to the conclusion that external forces must have caused the behavior.
While the proposition of Riemer (2018) discussed a connection between altered
crossmodal temporal recalibration and the development of psychotic symptoms, it only
described a specific mechanism of altered sensorimotor temporal recalibration in the
development of a specific symptom of psychosis, namely delusions of control, and thus offers
no generalized framework. To our knowledge, no theoretical approach trying to connect
sensory-sensory temporal recalibration and the development of psychotic symptoms exists to
date. This lack of a theoretical account might lead to poor hypothesis generation and testing,
possibly resulting in a rather result-driven study approach failing to connect experimental
findings with phenomenological constructs of psychosis. We argue that a crucial next step is
trying to connect existing work on multisensory temporal processing deficits in psychosis
with disorder models of psychosis, such as investigating potential links between impaired
multisensory temporal processing and the experience of anomalous percepts (see 4.2
Anomalous Perceptual Experiences as a Potential Link between Multisensory
Processing and Psychosis in the General Introduction) or altered inference mechanisms
(see 5.1 Causal Inference in the General Discussion). Such attempts of linking previous
findings with concepts of disorder models might be beneficial for generating hypotheses on a
potential key role of altered multisensory temporal integration and (potentially) crossmodal
temporal recalibration for psychosis.
4.3 Hypothesis 3: Associations between Temporal MSI, Temporal Recalibration and

99
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
Psychotic Symptoms
Finally, we aimed to replicate previous findings of correlations between multisensory
temporal processing and psychotic symptoms (Dalal et al., 2021; Di Cosmo et al., 2021; Ferri
et al., 2017, 2018; Foucher et al., 2007; Marsicano et al., 2022; Stevenson, Park, et al., 2017)
and further extend these findings to crossmodal temporal recalibration. We expected
associations between the general TBW, the cumulative as well as the immediate recalibration
effect and self-reports on psychotic symptoms and negative schemata.
Contrary to our expectation, we did not observe any significant correlation between
experimental and questionnaire data. Further, no Spearman rank correlation coefficient ρ
between the TBW and questionnaire scores approached our threshold of interest, i.e. ρ > .3.
This indicated that the general TBW, the cumulative as well as the immediate recalibration
effect showed no associations to anomalous perceptual experiences, hallucinations, paranoia,
passivity experiences and negative schemata about the self and others, suggesting that
temporal MSI as well as crossmodal temporal recalibration might not be directly linked to
psychotic symptoms.
4.3.1 Associations between the TBW and Psychotic Symptoms
Our findings are inconsistent with previous work on the multisensory TBW in
psychosis reporting significant associations between an enlarged TBW and psychotic
symptoms. Stevenson, Park, et al. (2017) observed that an enlarged AV TBW predicted
hallucination severity in patients with the diagnosis of a psychotic disorder. Foucher et al.,
(2007) observed an association between the AV TBW and symptoms of disorganization.
Further, associations between an enlarged TBW and higher schizotypy as well as symptoms of
hallucinations and disorganization in psychosis proneness have been reported, suggesting a
potential endophenotype (Dalal et al., 2021; Di Cosmo et al., 2021; Ferri et al., 2016, 2017,
2018; Marsicano et al., 2022; Zhou, Cui, et al., 2022).
Given the lack of differences in the TBW between our patient and control samples, it is
possible that we failed to observe correlations because the symptom load and in turn
perceptual-cognitive impairments of our outpatient sample might have been too low to
observe an enlarged TBW, which might have reduced the variance needed to detect
statistically significant correlations between the TBW and psychotic symptoms. However, our

100
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
patient sample reported significantly higher scores than healthy controls in all questionnaires,
therefore we argue that this minimizes that possibility.
However, our findings are consistent with studies reporting no associations between
the AV TBW and psychotic symptoms (Haß et al., 2017; B. Martin et al., 2013; Zhou, Lai, et
al., 2022) or schizotypal traits in healthy subjects (Muller et al., 2020; Zhou et al., 2020).
Further, several studies on the TBW in visual, i.e. unimodal stimuli also reported no
associations between the TBW and psychotic symptoms (Capa et al., 2014; de Boer-
Schellekens et al., 2014; Giersch et al., 2009; Grimsen et al., 2013; Tenckhoff et al., 2002).
This suggests that an enlarged TBW might not be directly related to psychotic symptoms,
especially in conditions where only visual stimuli are presented. This is however not
consistent with the findings of a meta-analysis by Ueda et al. (2018) reporting a significant
correlation between psychotic symptoms and altered temporal processing, which the authors
argue might be rooted in timing acceleration (Ueda et al., 2018). Crucially, only four studies
could be included in the meta-analysis of Ueda et al. (2018), we thus argue that their findings
should be interpreted with caution. Further research with larger sample sizes for robust
correlational testing is needed to investigate specific association patterns between psychotic
symptoms and uni- and multisensory temporal processing and to gather empirical support for
accounts of a potential role of altered temporal processing for disorder development (e.g.
Amadeo et al., 2022; Andreasen et al., 1999; Thoenes & Oberfeld, 2017).
4.3.2 Associations of Crossmodal Temporal Recalibration and Psychotic Symptoms
Our findings regarding a lack of associations between crossmodal temporal
recalibration and psychotic symptoms are consistent with a study in healthy subjects by Zhou
et al. (2020). Administering a SJ paradigm, Zhou et al. (2020) expected significant
associations between a reduced immediate recalibration effect and schizotypal and autistic
traits, but their results failed to support their expectation. These and our findings in patients
with the diagnosis of a psychotic disorder might suggest that (immediate) temporal
recalibration is not directly associated with psychotic symptoms, but more studies
corroborating this are needed. To our knowledge, the study by Zhou et al. (2020) is the only
published study investigating associations between psychotic symptoms/schizotypy and
crossmodal temporal recalibration. Reviewing findings of crossmodal temporal recalibration
in ASD/samples with autistic traits could possibly give hints for future hypothesis generation
in psychosis.

101
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
Noel et al. (2017) reported reduced immediate recalibration in ASD, suggesting a link
between ASD and recalibration processes. However, the authors did not investigate
correlations between the size of the immediate recalibration effect and symptoms of ASD
(Noel, De Niear, et al., 2017). Both Turi et al. (2016) and Zhou, Cui, et al. (2022) reported
correlations between impaired immediate temporal recalibration and increased autistic
symptoms, which however is not consistent with findings of Zhou et al. (2020), who failed to
observe associations between autistic traits in healthy individuals and immediate recalibration.
Moreover, Stevenson, Toulmin et al. (2017) reported significant correlations between
increased autistic traits and a reduced cumulative recalibration effect in a healthy student
sample.
In sum, while prior evidence suggested a link between crossmodal temporal
recalibration and symptoms of ASD (Noel, De Niear, et al., 2017; Stevenson, Toulmin, et al.,
2017; Turi et al., 2016; Zhou, Cui, et al., 2022), our findings did not reveal associations
between psychotic symptoms and both cumulative and immediate crossmodal temporal
recalibration. It is possible that impaired crossmodal temporal recalibration shows specific
associations with autistic symptoms but not so much to psychotic symptoms. Given the todate
scarcity of findings on crossmodal temporal recalibration in neurodevelopmental disorders –
especially in psychosis – and at least party contradictory findings on associations between
ASD/autistic traits and immediate temporal recalibration (Turi et al., 2016; Zhou, Cui, et al.,
2022; Zhou et al., 2020), further research on both cumulative and immediate temporal
recalibration in psychosis and ASD is needed to clarify if there are specific links between
crossmodal temporal recalibration and symptoms of ASD, psychosis or even both.
4.4 Limitations and Implications for Future Research
In addition to potential study limitations already mentioned earlier, i.e. the recruitment of a
potentially rather functional outpatient sample compared to previous studies, small sample
sizes for correlation analyses, and a large variability in experimental data in both groups, we
propose the following possible limitations and implications for further research.
Our patient and control samples differed significantly in education, with fewer patients
reporting higher education levels compared to controls. This is not surprising, since previous
studies reported that individuals with the diagnosis of a psychotic disorder were less likely to
achieve higher education levels (for a review and meta-analysis, see Dickson et al., 2020).

102
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
While recent findings suggested that multisensory processes might predict the development of
cognitive abilities in school children likely via benefits of multisensory learning environments
(Denervaud et al., 2020), how the highest achieved level of education in adults influences
multisensory processing in an experimental setting might be debatable – a question, which
requires future experimental investigation. Importantly, it can be argued that this group
difference in education did not impact our findings, since both groups showed similar levels
of temporal multisensory processing.
Our patient sample showed lower processing speed and vigilance compared to healthy
controls, as indicated by group differences in TMT and CPT-IP. Importantly, while vigilance
levels were overall lower in patients compared to controls, it did not decrease faster than in
healthy controls. When evaluating the potential influence of TMT and CPT-IP performance on
our behavioural data, we observed correlations between TMT-B completion times, CPT-IP
overall d’ score and the general TBW, indicating that longer TMT-B completion time and
lower CPT-IP d’ over d’ scores were associated with a larger TBW. This link between
processing speed, vigilance and the TBW is consistent with reports of impaired processing
speed and vigilance (Gebreegziabhere et al., 2022; Mesholam-Gately et al., 2009) and of an
enlarged TBW (Noel et al., 2018; Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021)
in psychosis, suggesting that psychosis could offer a link between our observed association
between TMT, CPT-IP and the general TBW. In contrast, we did not observe any association
of TMT and CTP-IP to our measures for crossmodal temporal recalibration. Crucially, since
no group differences in the general TBW and crossmodal temporal recalibration could be
observed in our study, it can be argued that group differences in TMT and CPT-IP might have
had limited impact on our behavioural findings.
During adaptation phases, we presented AV stimuli with a fixed SOA of 200ms, which can
be assumed to lie within the TBW of both the patient and control group. Presenting AV stimuli
with SOAs larger than the TBW decreases the likelihood of perceiving the stimuli as
belonging to the same event (Wallace et al., 2020; Wallace & Stevenson, 2014), potentially
reducing cumulative recalibration processes (Vroomen et al., 2004). As reported earlier, an
enlarged multisensory TBW in psychosis might lead to erroneous integration of AV stimuli
stemming from distinct events (Zhou et al., 2018). It might be interesting to present AV
stimuli during adaptation phases with an SOA inside the enlarged TBW reported in psychosis
but outside the typical TBW of healthy controls and to investigate if this impacts cumulative

103
CHAPTER III: TEMPORAL MULTISENSORY INTEGRATION & CROSSMODAL
TEMPORAL RECALIBRATION IN PSYCHOSIS
temporal recalibration differently in patients and healthy controls. In such an experimental
design, it could be a plausible speculation that patients with the diagnosis of a psychotic
disorder might show a cumulative temporal recalibration effect whereas healthy control might
not. Future studies should investigate the hypothesis if psychosis is associated with
maladaptive cumulative temporal recalibration in situations in which cumulative recalibration
should not occur.
4.5 Conclusion
In this study on temporal MSI and crossmodal temporal recalibration in psychosis, we
were unable to replicate previous findings of an enlarged TBW in psychosis (Noel et al., 2018;
Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021). Further, our study is the first to
investigate cumulative and immediate crossmodal temporal recalibration in psychosis. Our
findings indicate both intact cumulative and immediate AV recalibration and contrast prior
findings of impaired crossmodal recalibration in subjects with autistic traits and in ASD
(Noel, De Niear, et al., 2017; Stevenson, Toulmin, et al., 2017), a neurodevelopmental
disorder sharing deficits in temporal MSI with psychosis (Zhou et al., 2018). Finally, we did
not observe associations between temporal MSI as well as crossmodal temporal recalibration
and psychotic symptoms, providing no support for accounts of a potential role of impaired
temporal multisensory processing for the development of psychotic symptoms (e.g. Amadeo
et al., 2022; Andreasen et al., 1999; Thoenes & Oberfeld, 2017). Further research on
crossmodal temporal recalibration both in psychosis and ASD is needed to investigate a) if our
findings of intact crossmodal recalibration in psychosis can be replicated, b) if factors such as
symptom severity, cognitive impairments or task complexity influence temporal multisensory
processing in psychosis, and c) if patterns of impaired crossmodal temporal recalibration
potentially differ between psychosis and ASD, which would offer support for previous
findings on different underlying mechanisms for impaired multisensory temporal processing
in psychosis and ASD (Noel et al., 2018).

104
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Chapter IV:
Spatial Multisensory Integration &
Crossmodal Spatial Recalibration
in Psychosis (Study 3)

105
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
1 Introduction
1.1 Spatial Multisensory Processing
In everyday life, a multitude of sensory information originating from various spatial
positions needs to be continuously processed. Spatial relations between crossmodal stimuli,
such as the position of a ball bouncing at the pavement and the accompanying sound, are
crucial determinants for multisensory processing. Spatially close stimuli are more likely to
perceived as originating from the same source than spatially distant stimuli (Meredith & Stein,
1986; Spence, 2013). Spatial MSI describes the integration of two or more crossmodal
sensory signals alongside spatial dimensions, which often appear spatially disparate to a
certain extent due to e.g. differences in spatial resolution of the respective sensory organs
(Alais & Burr, 2004).
A well-known effect discussed to reflect spatial MSI is the VE. It describes the spatial
capture of the perceived location of a sound by a spatially disparate visual stimulus (Alais &
Burr, 2004; Radeau & Bertelson, 1974). It has been discussed that the higher spatial resolution
of the visual system compared to that of auditory system might be a central characteristic
leading to the sound location capture by the visual stimulus (Alais & Burr, 2004). Further, it
has been reported that this crossmodal capture process depends on stimulus reliability of the
respective stimuli: If the reliability of the sound increases in relation to the reliability of the
visual stimulus, the extent of AV integration decreases. The VE has been even found to
reverse when the reliability of the sound drastically exceeded the visual reliability, leading to a
visual stimulus capture by the sound (Alais & Burr, 2004). While the VE has been
investigated most in AV stimuli, spatial integration has also been reported in other crossmodal
stimulus combinations such as audio-tactile or visuo-tactile stimuli (e.g.
Bruns & Röder, 2010; Caclin et al., 2002; Samad & Shams, 2016).
Analogue to multisensory processes in the temporal domain (see 1.1 Temporal
Multisensory Processing in Chapter III), exposure to a crossmodal spatial conflict does not
only induce “on-line” integration, but can also lead to crossmodal spatial recalibration. A
prominent example is the so called cumulative ventriloquist aftereffect (VAE), which
describes a shift in unisensory sound localization induced by previous, prolonged exposure to
a consistent AV spatial conflict. This prolonged exposure leads to a shift in unisensory sound
localization in the direction of the visual stimulus while the visual stimulus is no longer
present (for a review, see Chen & Vroomen, 2013; Radeau & Bertelson, 1974). This

106
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
cumulative crossmodal recalibration is thought to reflect adjustment processes of auditory
cortical maps to shifts in spatial correspondences between crossmodal signals. These shifts
can occur as consequences of e.g. changes in the environment such as stepping outside of a
building or changes in spatial relations between sensory organs due to bodily growth. As such,
it has been argued that crossmodal recalibration reflects the aim of the perceptual system to
reduce the discrepancy between the senses and maintain a coherent percept (Chen &
Vroomen, 2013). The cumulative VAE has been studied extensively in AV (Chen & Vroomen,
2013), but also e.g. in audio-tactile (Bruns, Liebnau, et al., 2011; Bruns, Spence, et al., 2011)
or visuo-tactile stimuli (Samad & Shams, 2018). Apart from the cumulative spatial
recalibration effect induced by repeated exposure to an crossmodal spatial conflict, a rapid
crossmodal spatial recalibration effect after a single exposure to an AV spatial conflict has also
been observed, the so called immediate VAE (Wozny & Shams, 2011). This finding indicated
that the perceptual system is able to rapidly adapt to crossmodal spatial discrepancies and
suggests a high plasticity of the perceptual system (Wozny & Shams, 2011). Crucially, Bruns
& Röder (2015) observed cumulative and immediate spatial recalibration in the same
experiment, with both effects occurring on partly different time scales. Based on their
findings, Bruns & Röder (2015) proposed that cumulative and immediate recalibration reflect
distinct underlying processes with both effects influencing sound localization.
Previous evidence has suggested that although spatial MSI and crossmodal spatial
recalibration are separate processes, they might partly be linked to each other. As mentioned
earlier (see 1.1 Temporal Multisensory Processing in Chapter III), recent studies have
indicated that spatial MSI might be associated with immediate spatial recalibration with both
processes being based on common underlying neural substrates, whereas cumulative spatial
recalibration might be a relatively distinct process (Bruns et al., 2022; Park & Kayser, 2019;
Rohlf et al., 2020). Further, recent evidence has suggested that both spatial MSI and
immediate spatial recalibration develop earlier than cumulative spatial recalibration,
supporting the notion of a relative dissociation of spatial MSI and cumulative spatial
recalibration (Rohlf et al., 2020).
In sum, the perceptual system continuously processes crossmodal information and
utilizes the spatial relations of crossmodal cues to infer they belong to a unitary event and to
recalibrate for crossmodal spatial conflicts (Chen & Vroomen, 2013; Spence, 2013).
Analogue to the previously mentioned proposition in the temporal domain (see 1.1 Temporal

107
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Multisensory Processing in Chapter III), it could be argued that erroneous spatial
integration and/or recalibration of crossmodal stimuli might impact the creation of holistic and
stable representations of the environment and the self and is potentially associated with
disintegration of sensory information in psychosis (Postmes et al., 2014; Uhlhaas & Mishara,
2006).
1.2 Psychosis and Spatial Multisensory Integration
Psychosis has been found to be associated with unisensory processing deficits such as
impaired visuospatial perception (Hardoy et al., 2004) or deficient auditory pitch detection
and sound localization (Gold et al., 2012; Perrin et al., 2010; Sardari et al., 2022). This raises
the question if impaired unisensory spatial processing might impair multisensory spatial
processing in psychosis. In the temporal domain, deficits in AV MSI in psychosis have been
reported to be not entirely explainable by auditory or visual processing deficits, suggesting
specific deficits in multisensory compared to unisensory processing in psychosis (Stevenson,
Park, et al., 2017). To date, it however remains unclear if and how unisensory processing
deficits reported in patients with the diagnosis of a psychotic disorder (Carter et al., 2017;
Gold et al., 2012; Hardoy et al., 2004; Javitt, 2009a; Javitt & Freedman, 2015) might
influence spatial MSI in psychosis.
While there has been a considerable amount of studies on multisensory processing of
social, i.e. linguistic and emotional (Lin et al., 2020; Tseng et al., 2015) and temporal (Zhou et
al., 2018) information in psychosis, spatial multisensory processing has been scarcely
investigated in patients with the diagnosis of a psychotic disorder.
An earlier study by de Gelder et al. (2003) investigated spatial MSI in patients with the
diagnosis of a psychotic disorder via a ventriloquist paradigm with short sequences of simple
AV stimuli. In this first experiment of the study of de Gelder et al. (2003), auditory
localization responses were similarly captured by concurrently presented visual stimuli in
patients compared to healthy controls, suggesting an intact VE. In contrast, the second
experiment in the study of de Gelder et al. (2003) indicated significantly reduced integration
of AV speech stimuli in patients compared to controls in a McGurk (McGurk & MacDonald,
1976) paradigm. de Gelder et al. (2003) proposed that MSI of linguistic information is
impaired in psychosis, but basic spatial MSI might be intact. This proposition of intact spatial
MSI in psychosis by de Gelder et al. (2003) is supported by three further studies using an AV

108
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
far-near judgement paradigm, which reported similar crossmodal facilitation in patients with
the diagnosis of a psychotic disorder compared to healthy controls. Importantly, unisensory
performance in visual and auditory trials was impaired in patients compared to controls,
suggesting that crossmodal stimulus presentation might ameliorate unisensory processing
deficits (Stephen et al., 2013; Stone et al., 2011, 2014).
A recent study by Noel et al. (2020) investigated visuo-tactile spatial integration in
psychosis and ASD. Both clinical groups showed similar tactile localization performance in
spatially congruent and incongruent crossmodal conditions compared to healthy controls,
suggesting intact spatial visuo-tactile integration with simple stimuli. In their second
experiment, Noel et al. (2020) used visual stimuli either moving towards or away from the
participant to investigate visuo-motor spatial integration depending on the individual’s
peripersonal space. Contrary to their expectation, visuo-tactile integration was not differently
affected in psychosis compared to controls depending on whether stimuli were within vs.
outside the peripersonal space, with only the ASD group showing a smaller peripersonal space
in which visuo-tactile integration occurred. While this suggested intact visuo-tactile
integration in psychosis in the peripersonal space (Noel et al., 2020), this contrasted earlier
findings of altered sensorimotor integration and weakened borders of peripersonal space in
psychosis (for a review, see Noel, Cascio, et al., 2017).
While the above mentioned studies suggested intact spatial MSI in simple AV and
visuo-tactile stimuli in psychosis (de Gelder et al., 2003; Noel et al., 2020; Stephen et al.,
2013; Stone et al., 2011, 2014), AV target detection studies in psychosis reported inconsistent
findings. Wynn et al. (2014) reported similar AV target detection in patients compared to
controls, whereas Williams et al. (2010) observed a reduced crossmodal facilitation effect
during target detection in patients compared to controls. Further, Williams et al. (2010)
observed significant associations between reduced crossmodal facilitation and negative
symptoms, suggesting a link between MSI of AV information and symptoms of psychosis.
Given the scarcity of studies on spatial MSI using simple stimuli in psychosis, the
existing evidence suggesting intact spatial integration in psychosis (de Gelder et al., 2003;
Noel et al., 2020; Stephen et al., 2013; Stone et al., 2011, 2014) to date should be interpreted
cautiously. The comparability of the few published studies might be limited due to variations
in experimental paradigms, study designs, and involved sensory modalities. Further, the only
published study on spatial AV integration in psychosis administering a VE paradigm (de

109
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Gelder et al., 2003), one of the most frequently applied operationalization of spatial
integration in healthy participants (Bruns, 2019), deviated from classical VE paradigms by
presenting series of sound and flash stimuli rather than single pairs of AV stimuli. In typical
VE experiments, crossmodal stimuli are usually presented with randomized degrees and
directions of spatial conflicts to prevent cumulative recalibration (Bruns, 2019). It is possible
that localization responses in the study by de Gelder et al. (2003) were influenced by
recalibration processes due to the presentation of sequential AV stimuli with fixed spatial
disparities. Thus, we aimed to replicate earlier findings of intact spatial MSI in patients with
the diagnosis of a psychotic disorder by administering a VE paradigm with single pairs of AV
stimuli.
As mentioned throughout this dissertation as an overarching open issue, the question to
date remains if deficient MSI in psychosis might be domain-specific, i.e. observable in
linguistic, emotional, temporal and sensorimotor but not necessarily simple spatial stimuli
(Lin et al., 2020; Noel, Cascio, et al., 2017; Tseng et al., 2015; Zhou et al., 2018), or rather
reflect a global impairment. A global deficit in MSI, i.e. impairments across all domains and
already observable in simple stimulus conditions and tasks, could e.g. be rooted in an altered
global crossmodal binding tendency (Odegaard & Shams, 2017). Crucially, temporal and
spatial MSI have been reported to be stable but dissociated processes in a study by Odegaard
& Shams (2016). This speaks against any assumption that a deficit in temporal MSI in
psychosis (Zhou et al., 2018) might imply that spatial MSI could also be impaired. With our
study on spatial multisensory processing in psychosis outlined in this chapter of the
dissertation, we aimed to add to the body of evidence on MSI in psychosis necessary to
address the above mentioned overarching issue of impairment globality vs. specificity.
1.3 Psychosis and Crossmodal Spatial Recalibration
While previous studies suggested intact AV (de Gelder et al., 2003; Stephen et al., 2013;
Stone et al., 2011, 2014) and visuo-tactile (Noel et al., 2020) spatial MSI in patients with the
diagnosis of a psychotic disorder, to our knowledge no published study investigated
crossmodal, i.e. sensory-sensory spatial recalibration in psychosis.
Previous studies on spatial recalibration in psychosis focused on sensorimotor rather
than sensory-sensory processes and suggested impaired sensorimotor recalibration. A study by
Bartolomeo et al. (2020) showed deficient visuomotor recalibration in patients with the

110
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
diagnosis of a psychotic disorder compared to healthy controls when reaching a target in a
prism adaptation paradigm. Crucially, impaired performance was observed during and after
prism adaptation but not during baseline, suggesting deficits specific for visuomotor learning
in psychosis (Bartolomeo et al., 2020). Rösler et al. (2015) observed impaired saccadic
remapping in psychosis during a task, in which the target stimulus shifted in position after
saccade initiation. Further, impaired remapping in patients with the diagnosis of a psychotic
disorder was significantly associated with severity of psychotic symptoms, suggesting a link
between visuomotor recalibration processes and psychosis (Rösler et al., 2015). Ferri et al.
(2016) showed altered proprioceptive processing and touch remapping in psychosis proneness
in a tactile TOJ paradigm, during which two tactile stimuli were presented on the hands in a
crossed and uncrossed condition.
While the above discussed studies suggested impaired sensorimotor recalibration
processes in psychosis, the findings of two other studies however showed a different alteration
pattern. Bansal et al. (2019) observed similar perceptual motor learning in patients with the
diagnosis of a psychotic disorder and healthy controls. Subjects had to reach to a visual target
with a cursor in a baseline condition, under an adaptation condition with rotated movement
behaviour of the cursor and a generalization condition with rotated cursor movement and
novel target positions. Patients and controls performed similar on baseline and during
adaptation, but patients failed to generalize to novel target positions, suggesting impaired
transfer of perceptual motor learning in psychosis (Bansal et al., 2019). Lencer et al. (2017)
investigated saccadic remapping with shifting targets after saccade initiation and observed
similar adaptation amplitude in patients with the diagnosis of a psychotic disorder and healthy
controls. While this contrasted the findings of previous saccade remapping studies in
psychosis (Rösler et al., 2015), Lencer et al. (2017) observed a significantly slower adaptation
speed and higher amplitude variability in patients compared to controls.
In sum, previous studies suggested altered sensorimotor and perceptual motor learning
processes in psychosis, which might however manifest in diverse parameters of motor
learning. The extent of e.g. visuomotor recalibration might be impaired or intact depending on
the experimental task, while deficits might also manifest in learning rate, precision or transfer.
Crucially, all of the above studies indicating altered spatial recalibration processes during
perceptual motor learning in psychosis, but evidence whether deficient spatial recalibration

111
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
might also be observed in non-proprioceptive crossmodal, i.e. sensory-sensory stimuli is
lacking.
While prior evidence suggested intact spatial MSI in psychosis (de Gelder et al., 2003;
Noel et al., 2020; Stephen et al., 2013; Stone et al., 2011, 2014), this does not allow direct
inferences about whether crossmodal spatial recalibration might be intact, especially in light
of previous evidence suggesting at least a partial dissociation between spatial MSI and
crossmodal (cumulative) spatial recalibration (Bruns et al., 2022; Park & Kayser, 2019; Rohlf
et al., 2020). We argue that it might be theoretically possible that the integration of simple AV
information could be intact in psychosis, but the remapping of auditory representations
depending on prior exposure to AV conflicts, i.e. crossmodal spatial recalibration, could be
impaired – analogue to findings in sensorimotor recalibration processes (e.g. Bartolomeo et
al., 2020; Ferri et al., 2016; Rösler et al., 2015). If sensory-sensory recalibration processes
might be impaired in psychosis, we argue that this could reflect an impairment to create and
maintain a coherent and stable representation of the environment, similar to discussions on
representations of the own body in psychosis (Postmes et al., 2014). As such, this could
drastically alter the experience of the surrounding world up to potentially confusing and
distressing percepts. Since no published study investigated AV spatial recalibration in
psychosis, we aim to fill this gap to follow up on the research question if a) both spatial MSI
and recalibration are intact in psychosis or b) if spatial recalibration is impaired or c) if even
both spatial multisensory processes are impaired. The former would rather support the
assumption of domain-specificity of impaired multisensory processes, i.e. deficits in
linguistic, emotional (Lin et al., 2020; Tseng et al., 2015), temporal (Zhou et al., 2018), and
sensorimotor (Bartolomeo et al., 2020; Ferri et al., 2016; Noel, Cascio, et al., 2017; Rösler et
al., 2015) but not in spatial processes. The latter would offer support for an assumption of a
global deficit and of an a universally impaired underlying mechanism of multisensory
processing in psychosis.
1.4 Research Question
In this study, we investigated spatial MSI and crossmodal spatial recalibration in
psychosis using simple AV stimuli. We aimed to investigate whether psychosis is associated
with intact spatial ventriloquism, which would replicate earlier findings by de Gelder et al.
(2003), or if spatial ventriloquism is altered in psychosis. Further, we investigated if
crossmodal spatial recalibration, measured via the cumulative and immediate VAE, is altered

112
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
or intact in psychosis. To our knowledge, our study is the first to investigate the VAE in
psychosis. We therefore aimed to extend previous findings on altered spatial recalibration in
psychosis in the sensorimotor domain (e.g. Bartolomeo et al., 2020; Ferri et al., 2016; Rösler
et al., 2015) to AV stimuli. Finally, we investigated associations between spatial MSI,
cumulative as well as immediate spatial recalibration and self-reports of psychotic symptoms
and negative schemata.
Patients with the diagnosis of a psychotic disorder and healthy controls localized
auditory stimuli presented with one of two frequencies either in unimodal auditory (UA) or
AV trials. During AV trials, the visual stimulus was either presented with a fixed spatial
distance to the left or right of the sound depending on the sound frequency of the auditory
stimulus, resulting in two sound frequency-specific AV spatial conflicts (paradigm adopted
from Bruns & Röder, 2015). For each frequency, we calculated the deviance of sound
localization responses in AV trials from the veridical sound position, i.e. the VE reflecting
spatial MSI. Further, per frequency we calculated the deviance of sound localization
responses in UA trials from the veridical sound position as a function of repeated exposure to
AV spatial conflicts, i.e. the cumulative VAE reflecting cumulative spatial recalibration, and
as a function of AV spatial conflicts during AV trials in the immediate stimulus history, i.e. the
immediate VAE reflecting immediate spatial recalibration.
Given the scarcity of findings in AV spatial MSI in psychosis, especially regarding its
potentially most frequently applied operationalization via the VE (Bruns, 2019), we aimed to
replicate the findings of de Gelder et al. (2003) and - in a broader context - those of other
studies on spatial MSI in psychosis (Noel et al., 2020; Stephen et al., 2013; Stone et al., 2011,
2014). Thus, we expected our patient sample to show intact spatial MSI, reflected by a
comparable VE size in patients compared to healthy controls. Based on findings of impaired
sensorimotor recalibration in psychosis (e.g. Bartolomeo et al., 2020; Ferri et al., 2016; Rösler
et al., 2015), we expected to observe altered spatial recalibration in patients with the diagnosis
of a psychotic disorder. However, in light of previous findings on a dissociation of cumulative
spatial recalibration and spatial MSI as well as evidence that immediate spatial recalibration
and spatial MSI might be based on the same underlying processes (Bruns et al., 2022; Park &
Kayser, 2019; Rohlf et al., 2020), we expected different patterns for cumulative and
immediate spatial recalibration. We expected to observe altered cumulative recalibration,
indicated by a difference in the size of the cumulative VAE, but intact immediate spatial

113
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
recalibration, indicated by a comparable size of the VAE, in patients with the diagnosis of a
psychotic disorder compared to healthy controls. Finally, we explored associations between
the VE, the cumulative as well as the immediate VAE and anomalous perceptual experiences,
hallucinations, paranoid delusions, passivity experiences as well as negative schemata.
2 Methods
2.1 Participants
We recruited 35 patients with the diagnosis of a psychotic disorder via flyers in
outpatient clinics and social care centers as well as contact data bases from earlier studies with
consent for further contact and 32 healthy controls via online recruitment services from the
University of Hamburg. 3 patients cancelled and 3 additional patients discontinued the
participation. Further, we excluded 1 participant from the healthy control group and 2 from
the patient group for not being able to sufficiently execute the experimental task (see 2.4 Data
Analysis). The final sample therefore consisted of 27 patients with the diagnosis of a
psychotic and 31 healthy controls (see Table 5 for demographic data). Participants differed
significantly in age, with patients showing a higher mean age (M = 41.0, SD = 10.6) than
healthy controls (M = 32.3, SD = 14.6), t(59) = 2.54, p = .013, Cohen’s d = 0.67. Groups did
not differ regarding the distribution of gender, Χ2(2) = 2.22, p = .330, φ = 0.20, or education,
Χ2(3) = 4.47, p = .215, φ = 0.28.
Patients were included if they fulfilled the DSM-V (American Psychiatric Association,
2022) criteria for schizophrenia or schizoaffective disorder. Patients were excluded if they had
a comorbid autism spectrum disorder. Healthy participants were excluded if they had a past or
present psychiatric disorder or a family history of first degree relatives with the diagnosis of a
psychotic disorder. General exclusion criteria consisted of dementia or other neurological
disorders, acute suicidality, substance abuse disorder in the last 6 months, uncorrected sight or
hearing impairment as well as inability to give consent or understand study instructions due to
health status or language barriers.
Participants gave written informed consent prior to participation and received 10€/hour
or course credits as compensation. The study was performed by the standards of the
Declaration of Helsinki and was approved by the Local Ethics Committee of the Faculty of
Psychology and Human Movement Science, University of Hamburg.

114
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Table 5
Demographic and Diagnostic Data Separated by Group
Patients Healthy Controls
n 27 31
Age, M (range) 41.0 (20-58) 32.3 (18-65)
Gender, n (%)
female male
diverse
13 (48.1)
14 (51.9)
0
19 (61.3)
11 (35.5)
1 (3.2)
Education, n
9 years
10 years 12-13
yearsa
university degreeb
0
8
12
7
1
3
18
9
CAPS, M (SD) 9.9 (6.7) 2.2 (2.4)
LSHS-E, M (SD) 22.3 (11.3) 4.4 (4.4)
PCL, M (SD) 81.7 (56.4) 21.3 (18.7)
Passivity experiences, M (SD) 5.5 (4.4) 0.3 (0.5)
BCSS n.S., M (SD) 6.9 (4.9) 2.0 (2.1)
BCSS n.O., M (SD) 7.9 (6.1) 3.3 (3.9)
Notes. N = 58. CAPS = Cardiff Anomalous Perception Scale, total score; LSHS-E = Launey-Slade Hallucination
Scale-Extended, total score; PCL= Paranoia Checklist, total score; BCSS n.S. = Brief Core Schema Scales,
negative self subscale; BCSS n.O. = Brief Core Schema Scales, negative other subscale.
a due to changes in German education law in 2007, the years of education for acquire the Abitur (A-level/high
school equivalent) vary between 12-13 years depending on school and Bundesland; b university degree: Bachelor
level or higher.

115
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
2.2 Stimuli and Experimental Paradigm
The experimental paradigm was adapted from Bruns & Röder (2015). Stimulus
presentation was controlled and participant responses were recorded by means of the Neurobs
Presentation® Software (Version 22; Neurobehavioural Systems Inc., Berkeley, California,
USA).
Stimuli were presented in a dark and sound-attenuated room using a custom built setup
consisting of a semi-circular metal rack of 85cm radius, covered in an acoustically transparent
black curtain. Participants were seated at the center of the semi-circle and rested their head on
a chin rest at 90cm distance to the semi-circle. Auditory stimuli were presented via speakers
(ConceptC Satellit, Teufel GmbH, Berlin, Germany), positioned on the semicircle at ±4.5,
±13.5 and ±22.5 degrees from the center and slightly above eye level. Auditory stimuli
consisted of 750Hz and 3000Hz sinusoidal tones with a duration of 200ms (5ms rise and fall
time) and were presented at 65dB(A), measured at the subject’s head position. For each
presentation, auditory stimuli randomly varied within a range of 4dB(A) to account for any
potential variation in speaker transformation function. Visual stimuli were presented by means
of LED-panels (APA102C RGB Full Color LED control IC, iPixel LED, Shiji Lighting,
Shiyan, China) with 256 color LEDs in a horizontal row (LED diameter = 0.5 cm, spacing
between LEDs = 0.5 cm, 2.54 ppi), arranged in front of the curtain and at eye-level and
covered the entire horizontal length of the semi-circle. Visual stimuli consisted of red flashes
of single LEDs with a duration of 200ms. For sound localization response, participants used a
movable pointer attached below the chin rest. The pointer was equipped with two
potentiometers, measuring the X- and Y-coordinates (in degrees relative to the pointer origin)
of the pointer position. The X and Y coordinate of the current pointer orientation as well as the
response time was recorded as soon as the participant pressed a button on the tip of the
pointer.
Prior to the experimental runs with participants, precise AV timing was ensured via
calibrating the presentation times of speakers and LEDs using a photometer and adjusting for
technically induced latencies.
The experimental paradigm consisted of 240 UA and 240 AV trials, divided in three
blocks of 160 trials. Each combination of frequency, speaker position and trial type (UA or
AV) was presented 20 times over course of the experiment, resulting in 480 trials. UA and

116
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
AV trials were presented in pseudorandom order. The trial order was preset so that for each
frequency half of the UA trials were preceded by an AV trial with the opposite frequency and
the other half by an AV trial of the same frequency, not counting UA trials in between.
Further, for the 60 UA trials of one frequency preceded by an AV trial of the same frequency,
15 trials each were preceded with a same-frequency AV trial in the last 1-4 trials.
Each trial started with a white fixation point of a single LED at the center. To start each
trial with the approximately same pointer orientation, participants were instructed to point at
the fixation point and press the button. If the pointer orientation was within a horizontal range
of ±10 degrees relative to the fixation, the fixation point disappeared, followed by a
randomized ISI of 750-1500ms (uniform distribution). Otherwise participants had to re-orient
the pointer and press again. Depending on trial type, subsequently an auditory stimulus was
either presented alone at one of the speaker positions or together with a synchronous visual
stimulus, horizontally displaced at ±13.5 degrees relative to the auditory stimulus. For each
participant, the visual stimulus was always presented 13.5 degrees to the left relative to
sounds of one of the two frequencies (either 750Hz or 3000Hz) and 13.5 degrees to the right
relative to the other, resulting in two frequency-specific AV adaptation directions: leftward-
adaptation and rightward-adaptation. We balanced the allocation of frequency and
leftward/rightward-adaptation over participants in dependence of the participant’s subject
number in the Neurobs Presentation® script, allocating each participant automatically to one
of two adaptation direction groups: even subject numbers were allocated to the 750R/3000L
and odd numbers to 750L/3000R adaptation direction subgroup.
Participants were instructed to indicate the perceived position of the tone by orienting
the tip of the pointer towards the position and button press while ignoring any visual stimulus.
Following the button press, the next trial started with the fixation point. After 160 trials each,
participants could take a short break of 2-3 minutes. The start and end of each block was
announced by five flashes of the white fixation point of 500ms duration each.
2.3 General Procedure
The study consisted of two sessions, which each lasted about 1.25 to 1.5 hours and took place
on two different days.
The first session covered informed consent and diagnostic procedures. After discussing
informed consent, participants provided information about age, gender, education level,

117
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
potential sight or hearing impairment and respective corrections, potential psychiatric
diagnoses and their current status, illness duration of psychotic disorders, potential family
history of psychotic disorder, psychopharmacological medication, wakefulness, motivation,
stress level and substance consumption in the last 24 hours. Handedness was assessed using
the EHI (Oldfield, 1971), followed by the TMT Version A and B (Reitan & Wolfson, 1985) to
measure attention and processing speed. Subsequently, the in- and exclusion criteria regarding
psychiatric diagnoses were checked using the SCID-V (Beesdo-Baum et al., 2019). Healthy
controls were interviewed using the sections A “Affective Disorders” and B “Psychotic
Disorders”, followed by a screening for the remaining sections. If any of the screening
questions was scored with “yes”, the respective section was conducted. Patients with the
diagnosis of a psychotic disorder were also interviewed using sections A and B, but not with
the screening. Instead, the PSYRATS (Haddock et al., 1999) was administered to further
enquire more details about acoustic verbal hallucinations and delusions. Finally, the CPT-IP
(Nuechterlein et al., 2008) was administered to measure vigilance.
Between session, participants were asked to provide self-reports about usual substance
consumption, schemata about the self and others by means of the BCSS (Fowler et al., 2006),
anomalous perceptual experiences by means of the CAPS (Bell et al., 2006), hallucinations by
means of the LSHS-E (Lincoln et al., 2009; Siddi et al., 2019), paranoia by means of the PCL
(Freeman et al., 2005) and passivity experiences by means of the factor “bizarre experiences”
of the CAPE (Schlier et al., 2015; Stefanis et al., 2002) (a glossary of the instruments and
questionnaires used in this dissertation project can be found in Table A.1 in Appendix A).
Participants completed the questionnaires at home and returned them at the second session.
Potential questions could be clarified at the end of the second session.
The experimental paradigm (see 2.2 Stimuli and Experimental Paradigm) was
administered during the second session. The second session took place within 1-10 days after
the first session, depending on the individual participant’s schedule. Participants were
comfortably seated in a chair in the center of the experimental set-up and placed their chin on
the chin rest. Participants received experimental instructions and potential questions were
answered. Afterwards, the first block was started, followed by block two and three with short
breaks in-between. Over the whole course of the experiment, the experimenter was seated in
the adjacent control room and surveyed the experiment progress on a screen. After the
experimental run, participants were de-briefed and received participation compensation.

118
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
2.4 Data Analysis
Prior to data analysis, we checked whether participants were able to localize sounds in
appropriate relative position to each speaker. We fit a regression line over localization
responses depending on speaker location in UA trials separately for each frequency and per
participant. The regression line slope of each participant was then compared to the mean slope
per frequency and group. We chose UA trials for investigating the relationship between
localization performance and speaker position, since sound localization response in AV trials
can reasonably be expected to be more biased towards the concurrently presented visual
stimulus compared to UA trials. Based on this slope comparison, three participants (two
patients and one healthy control) were excluded for having a slope close to zero and more
than 1.5 SD below the average. Further, we plotted the localization responses relative to the
speaker positions in UA trials separately for both groups and frequencies to visualize
localization performance.
After data collection, we noticed that the allocation of the two the adaptation direction
subgroups (750R/3000L vs. 750L/3000R) did not result in a balanced distribution due to
technical difficulties (37 vs. 21). Importantly, the adaptation direction ratio was comparable in
patients (17 vs. 10) and healthy controls (20 vs. 11). Further, data analysis revealed that the
effect pattern was similar in both adaptation direction subgroups (see 3.1.7 Exploratory
Analysis of Non-Merged Data), so it can be assumed that this allocation imbalance did not
impact the results.
Potential group differences regarding age and distribution of gender and education
were analyzed by means of an independent t-test and Pearson Χ2-tests, respectively.
Experimental data was preprocessed and statistical analysis conducted using R Version
4.2.2 (R Core Team, 2022). The preprocessing steps were adapted from Rohlf et al., (2020).
To quantify the VE, the mean constant error, i.e. the mean deviation of the sound
localization response from the true sound location, during AV trials was calculated per
participant. Within each of the two experimental groups (patients and healthy controls), we
merged the data from both adaptation direction groups (750R/3000L and 750L/3000R) by
inverting the sign of the mean constant error of the second adaption direction group. This data
merging was done for all of the following preprocessing steps of the experimental data (see
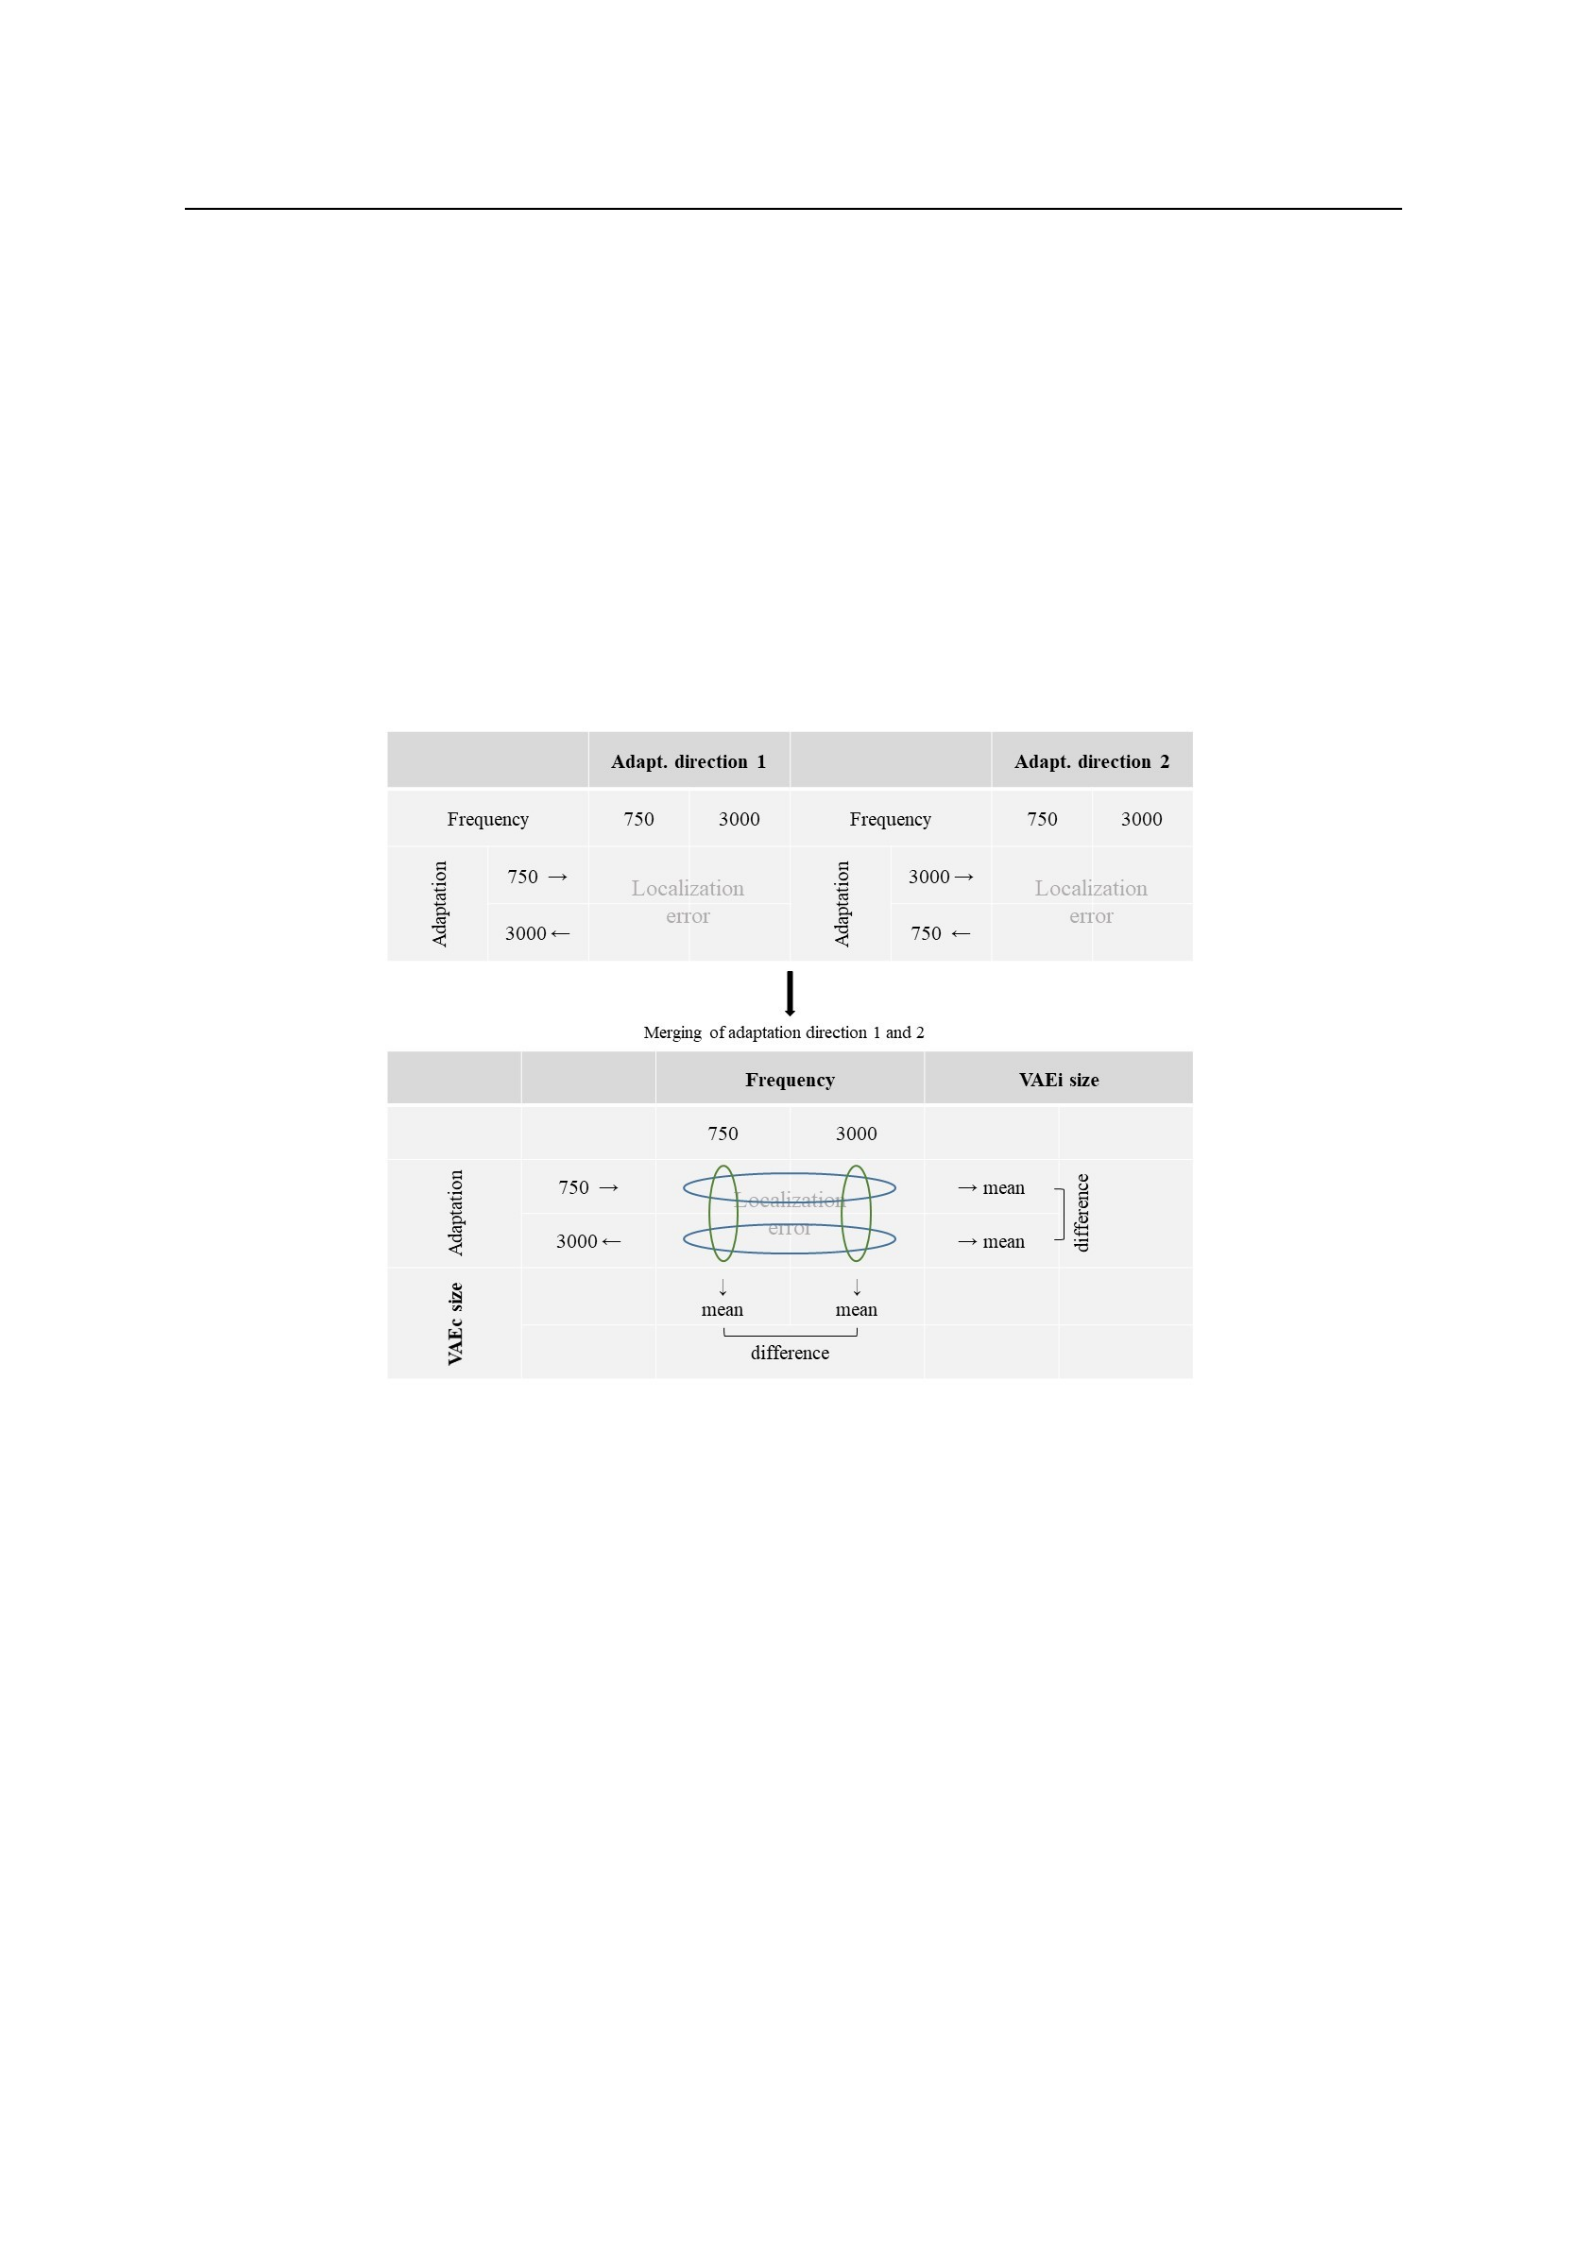
119
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Figure 8 for an illustration of the data merging process). A 2x2 mixed ANOVA with the
between-factor Group (patients vs. healthy controls) and the within-factor Direction (leftward-
adaptation vs. rightward-adaptation) on the mean constant error in AV trials was computed to
investigate group differences in VE. Further, we defined the size of the VE as the difference in
mean constant error between the leftward-adaptation and the rightwardadaptation AV trials
and quantified the VE size per participant accordingly.
Figure 8
Illustration of the Data Merging Process
Notes. VAEc = cumulative ventriloquist aftereffect; VAEi = immediate ventriloquist aftereffect. The constant
error was calculated as the mean deviation of the localization response from the veridical sound location. To
enable comparison over the entire groups of patients and healthy controls, the data from the second adaptation
direction (750 left/3000 right) subgroup was inverted in signs and then merged with the data from the first
adaptation (750 right/3000 left) subgroup. Afterwards, the cumulative VAE was calculated as the difference
between the mean constant errors in unimodal auditory trials of the leftward- vs. rightward adapted frequency.
The immediate VAE was calculated as the difference between the mean constant errors in unimodal auditory
trials preceded by a leftward-adaptation vs. rightward-adaptation audiovisual trial. Adapted from “Multisensory
Integration Develops Prior to Crossmodal Recalibration” by S. Rohlf, L. Li, P. Bruns & R. Röder, 2020, Current
Biology, 30(9), 1726-1732 (https://doi.org/10.1016/j.cub.2020.02.048).
To quantify the cumulative and immediate VAE, the mean constant error was
calculated for each UA trial per participant. After data merging of the two adaptation direction

120
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
groups (see paragraph above), both aftereffects were calculated accordingly. A 2x2 mixed
ANOVA with the between-factor Group (patients vs. healthy controls) and within-factor
Adapted Direction (leftward-adapted vs. rightward-adapted) on the mean constant error
during UA trials was computed to investigate group differences in cumulative VAE. Further,
we defined the size of the cumulative VAE as the difference in mean constant error between
UA trials with the leftward-adapted frequency and UA trials with the rightward-adapted
frequency and calculated it per participant.
A 2x2 mixed ANOVA with the between-factor Group (patients vs. healthy controls)
and the within-factor Direction of Preceding AV Adaptation (preceding leftward-adaptation vs.
rightward-adaptation AV trial) on the mean constant error was computed to investigate group
differences in immediate VAE. Additionally, we defined the size of the immediate VAE as the
difference in mean constant error between UA trials preceded by a leftwardadaptation AV trial
and UA trials preceded by a rightward-adaptation AV trial and calculated it per participant.
Additionally, the accumulation of the immediate VAE over the last one to four
consecutive preceding AV trials with one frequency was calculated. The difference in mean
constant error of the merged data (see above) between leftward- and rightward-adapted UA
trials preceded by the same frequency and different frequency for the last one to four
consecutive AV trials was calculated. Positive values indicated a shift of auditory localization
performance in direction of the preceding AV mismatch, negative values a shift in the opposite
direction of the preceding mismatch. Two separate mixed ANOVAs with the between-factor
Group (patients vs. controls) and the within-factor Consecutive Trial Number (one, two, three,
four) were calculated entering the size of the immediate VAE for UA trials preceded by an AV
trial with the same frequency and with the other frequency, respectively, followed by
Bonferroni-corrected post-hoc t-Tests. We applied the Greenhouse-Geisser correction
(Greenhouse & Geisser, 1959) in case of sphericity violations.
To check if the mapping of frequency and adaptation direction had a systematic effect
on localization performance, we additionally analyzed the non-merged data. For AV trials, we
calculated an exploratory mixed ANOVA with the between-factors Group (patients vs. healthy
controls) and Adaptation Direction (750R/3000L vs. 750L/3000R) and the withinfactor
Frequency (750Hz vs. 3000Hz) entering the mean constant error in AV trials. For UA trials,
we calculated an exploratory mixed ANOVA with the between-factors Group (patients vs.
healthy controls) and Adaptation Direction (750R/3000L vs. 750L/3000R) and the

121
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
withinfactors Frequency (750Hz vs. 3000Hz) and Frequency of prior adaptation trail (same
vs. different) entering the mean constant error in UA trials.
Welch two sample t-tests were conducted to check for group differences in attention
and processing speed, entering TMT-A and -B completion times (in seconds). Further,
potential group differences regarding vigilance were investigated by means of a mixed
ANOVA on CPT-IP d’ scores with Group (patients vs. healthy controls) and Digit Load (2 vs.
3 vs. 4 digits) as factors, followed by post-hoc t-tests. The influence of any control variable on
the main dependent variables was estimated by means of Spearman’s rank correlation
coefficients (ρ) with Bonferroni-corrected p-values, if group differences in TMT or CPT-IP
were revealed.
CAPS, LSHS-E, PCL, passivity experiences and BCSS scores were compared between
patients and healthy controls by means of Welch two sample t-tests, separately for each of the
questionnaires.
To investigate associations between AV integration as well as recalibration and
psychosis-related constructs, Spearman rank correlation coefficients ρ with
Bonferronicorrected p-values were calculated between the size of the VE, cumulative VAE
and immediate VAE and questionnaires scores. For all correlations, Spearman rank correlation
coefficients ρ > .3 were defined as potentially meaningful for discussion and highlighted in
correlation matrices.
The above mentioned mixed ANOVAS, t-tests, and correlations were additionally
investigated by means of Bayesian hypothesis testing using standard priors in JASP Version
0.16.4 (Wagenmakers et al., 2018) with reported BF indicating evidence for either the null or
alternative hypothesis. Per convention, a BF of 1 is discussed to reflect no evidence. A BF
between 3-10 indicates moderate, between 10-100 strong, and >100 extreme evidence in favor
of the alternative hypothesis. Accordingly, a BF between 1/3-1/10 reflects moderate, between
1/10-1/100 strong, and <1/100 extreme evidence in favor of the null hypothesis (for a
complete BF classification scheme, see Wagenmakers et al., 2018). For two-tailed tests and
correlations we reported BF10, the BF describing evidence for the alternative relative to the
null hypothesis, and for mixed ANOVAS BFincl, the BF reflecting the posterior probability for
model inclusion for a factor or interaction term averaged over all candidate models
(Wagenmakers et al., 2018).
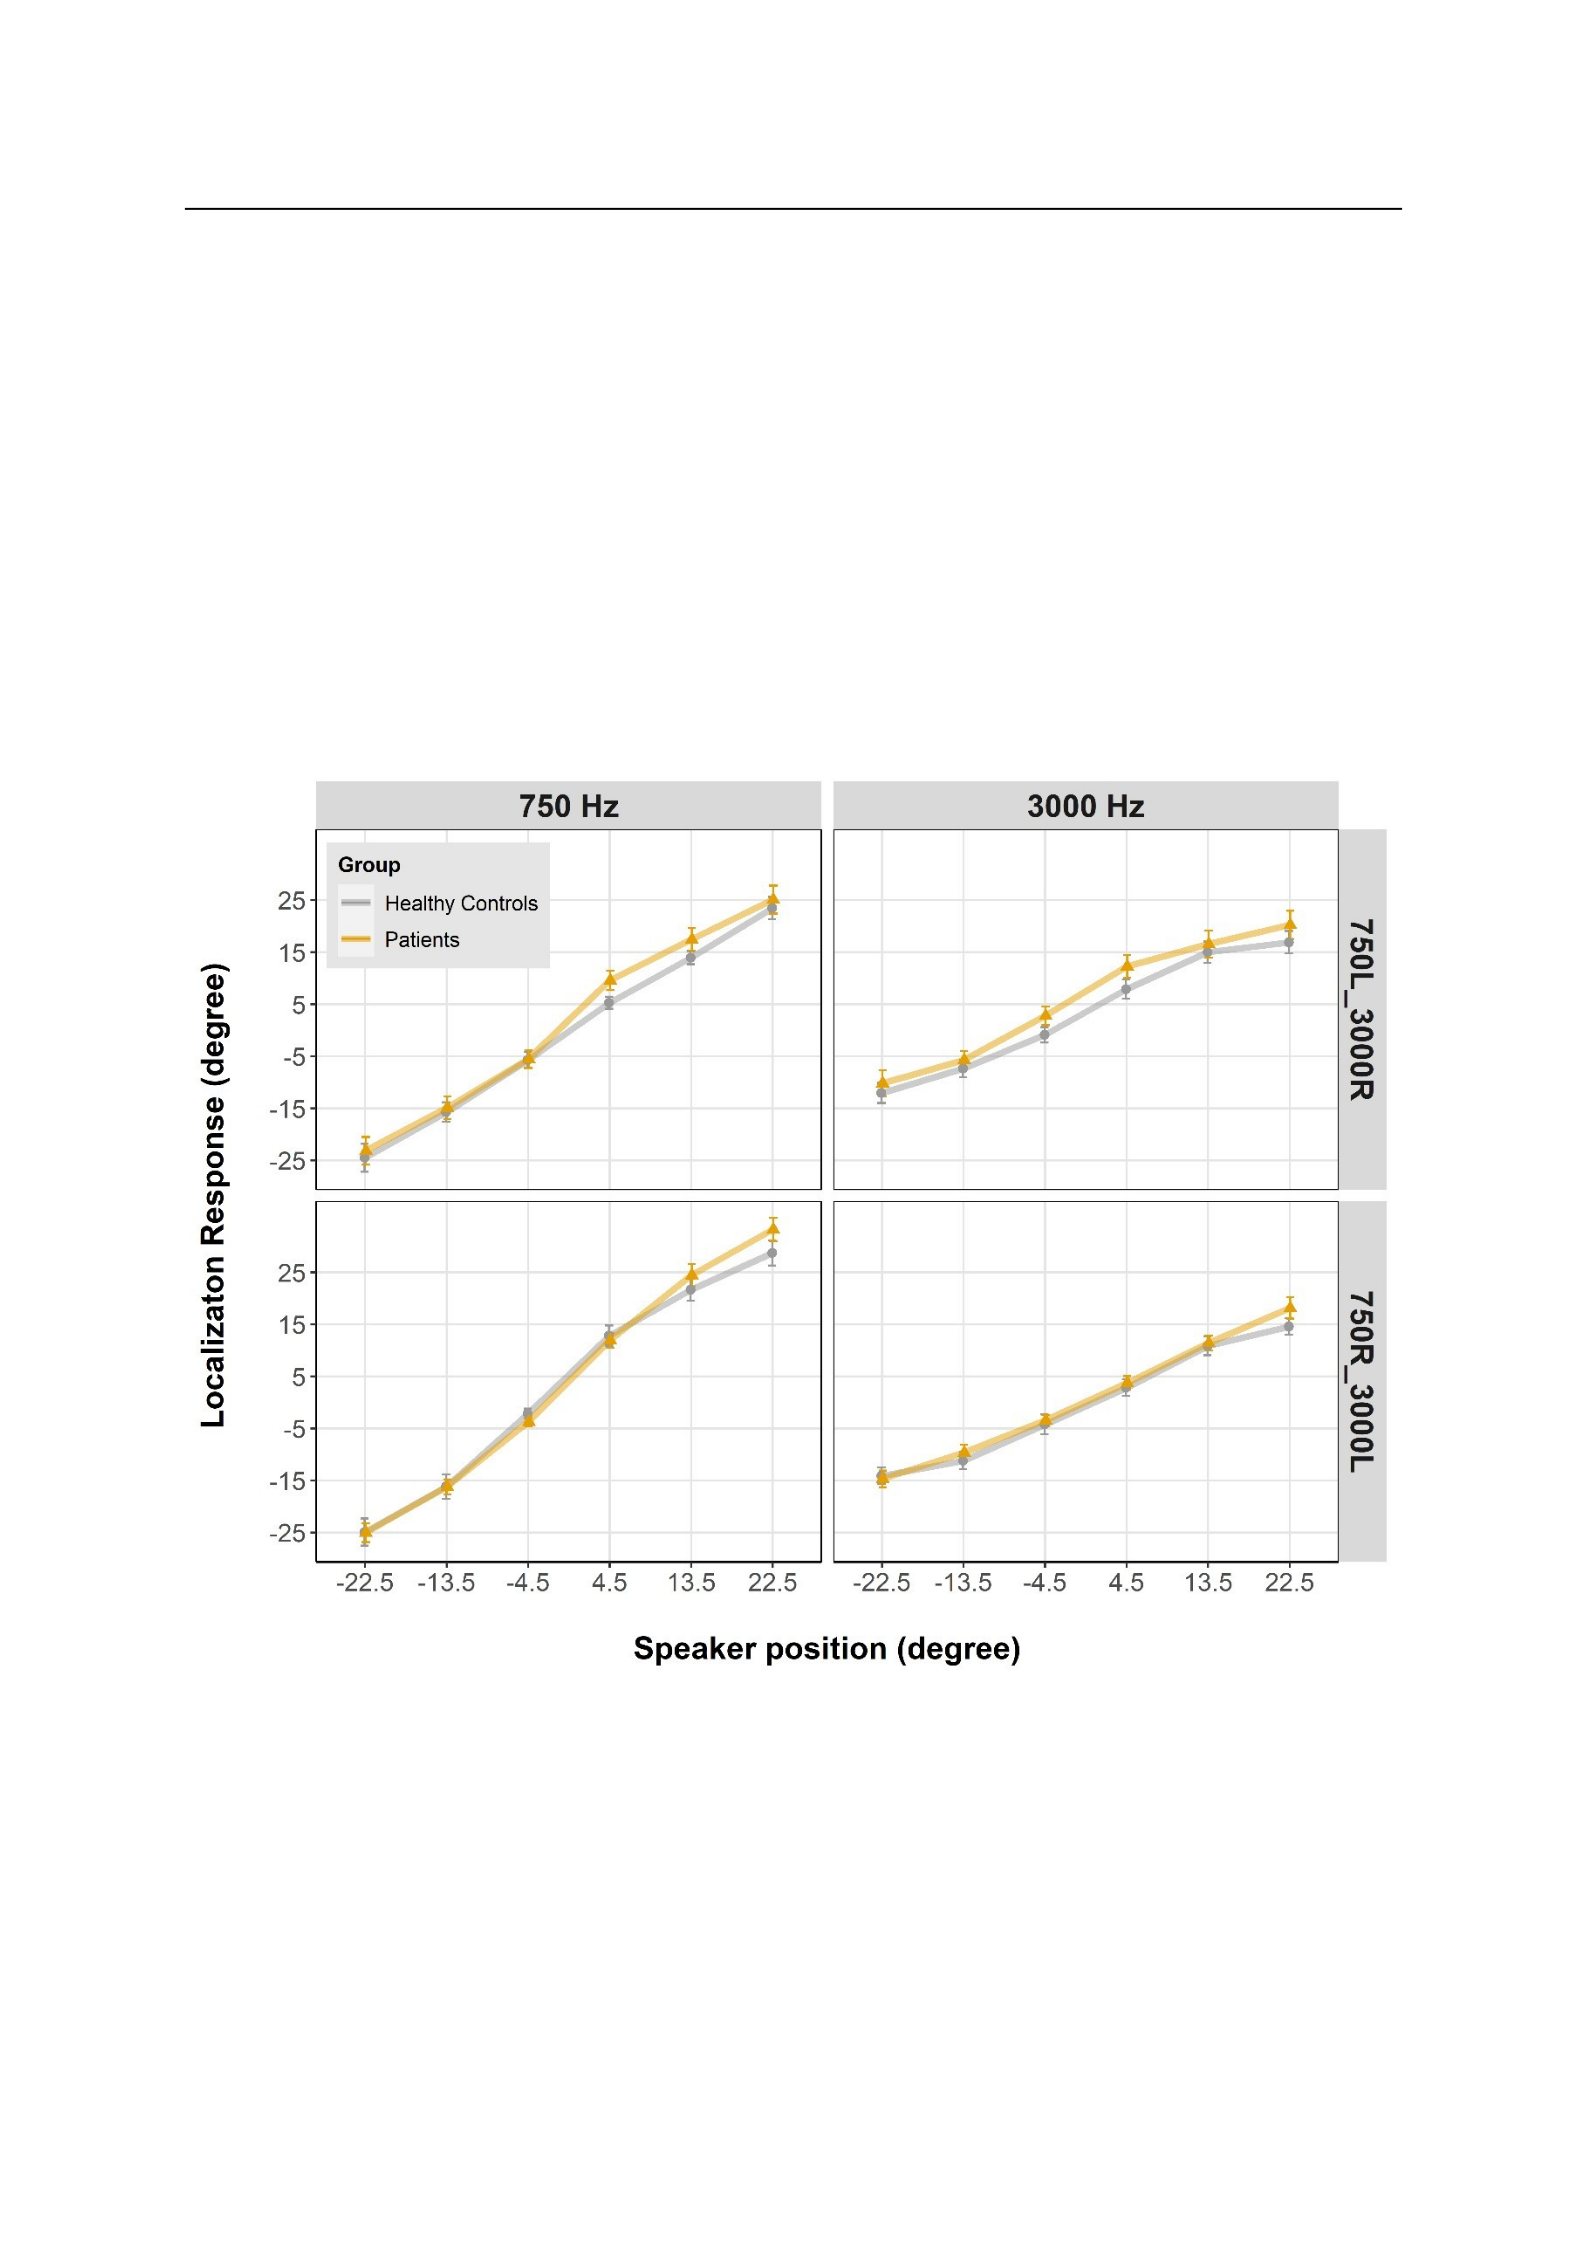
122
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
3 Results
3.1 Experimental Data
3.1.1 Localization Responses Relative to Speaker Positions
Figure 9 depicts the mean localization performance in UA trials relative to speaker
position for each group and adaptation direction combination. For all four combinations,
visual inspection implied a linear relationship between localization performance and veridical
sound location.
Figure 9
Localization Responses Relative to Speaker Position in Unimodal Auditory Trials
Notes. nHC = 31; nPAT = 27. Per group, the localization response in unimodal auditory trials relative to each
speaker position is shown for all combinations of frequency (750 Hz & 3000 Hz) and adaptation direction (750
Hz leftward/3000 Hz rightward & 750 Hz rightward/3000 Hz leftward). Error bars denote the SEM.
3.1.2 VE
A mixed ANOVA on the mean constant error in AV trials revealed a highly significant
main effect of Direction, F(1, 56) = 271.23, p < .001, η2p = 0.83, BFincl > 1000, indicating that
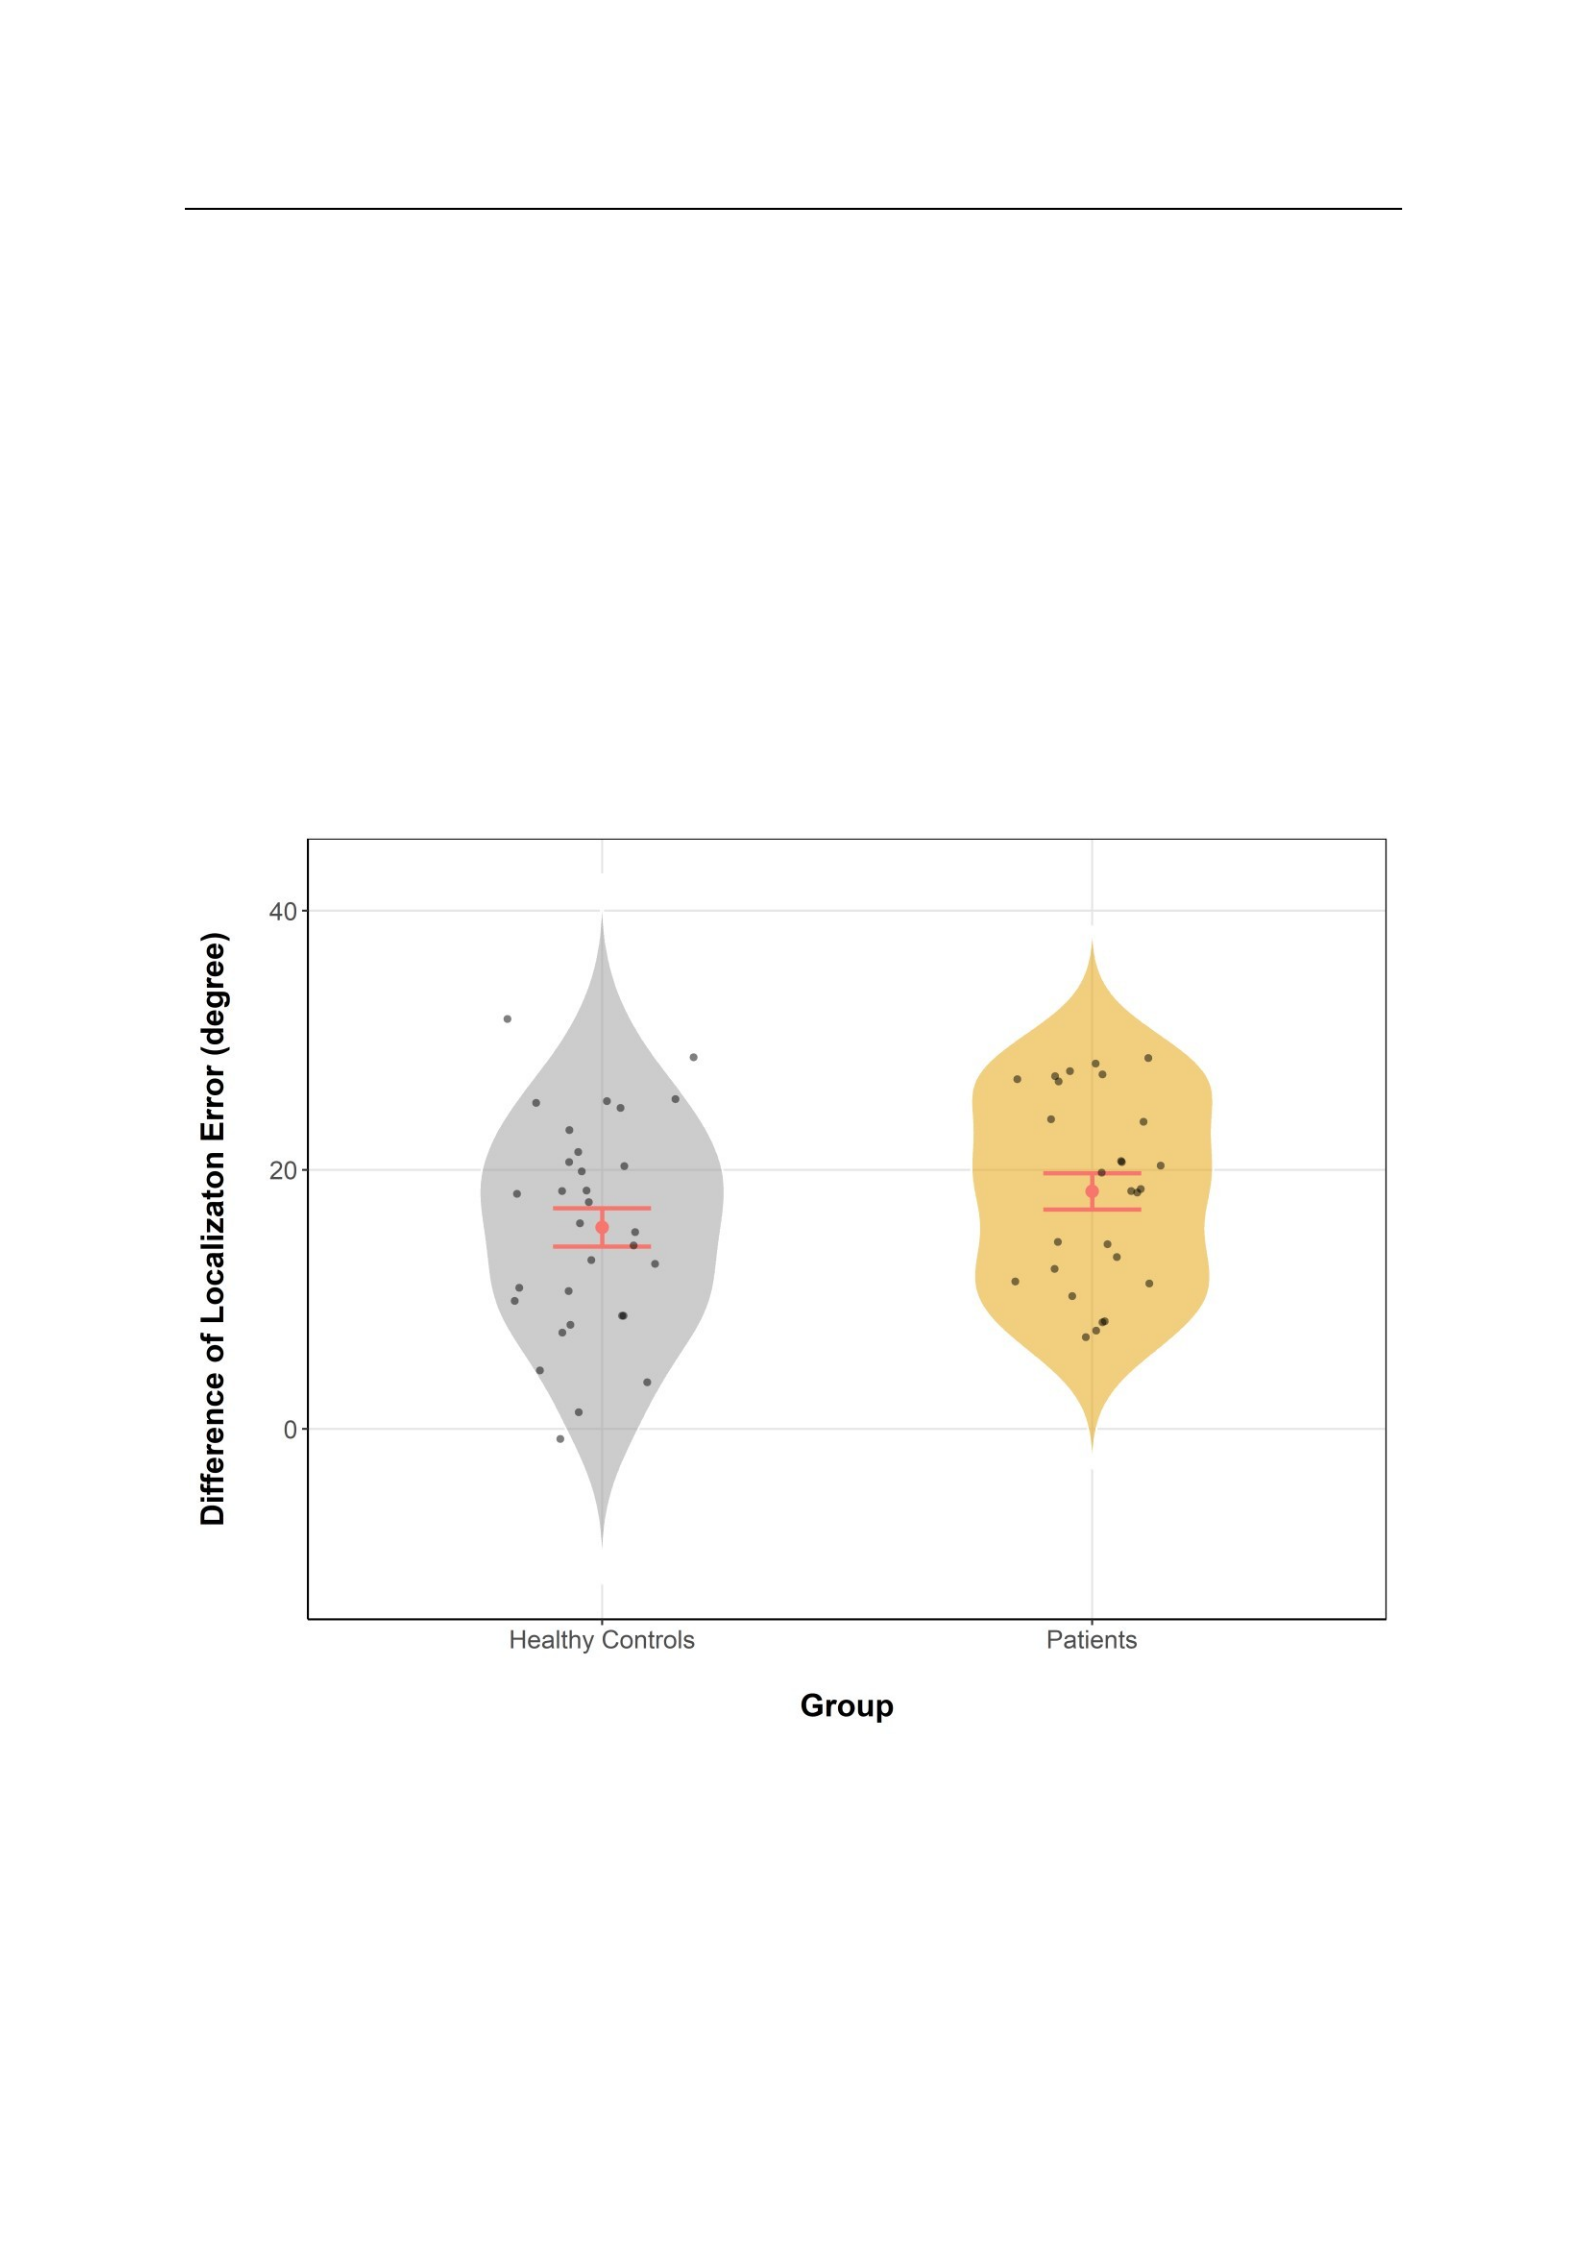
123
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
the mean constant error differed between leftward-adaptation (M = -8.73, SD = 4.69) and
rightward-adaptation (M = 8.13, SD = 5.78) AV trials. There was no main effect of Group,
F(1, 56) = 0.1, p = 0.757, η2p < 0.01, BFincl = 0.26, and no Group * Direction interaction, F(1,
56) = 1.83, p = 0.182, η2p = 0.03, BFincl = 0.53. This indicated that the VE size, i.e. difference
in mean constant error between leftward- and rightward-adaptation AV trials, did not differ
between patients (M = 15.35, SD = 7.27) and healthy controls (M = 15.57, SD = 8.23). Two
separate one-tailed t-Tests confirmed that each group independently showed a significant VE,
both p < .001 (see Figure 10 for the mean and distribution of VE size per group).
Figure 10
Mean and Distribution of Ventriloquist Effect Size
Notes. nHC = 31; nPAT = 27. The difference in the constant error between leftward- and the rightward-adapted
audiovisual trials is shown. Per group, the mean, error bars denoting the SEM, the value distributions as well as
the individual data points are depicted.

124
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
3.1.3 Cumulative VAE
A mixed ANOVA on the mean constant error in UA trials revealed a highly significant
main effect of Adapted Direction, F(1, 56) = 35.47, p < .001, η2p = 0.39, BFincl > 1000,
indicating that the mean constant error differed between leftward-adapted (M = -1.45, SD =
5.0) and rightward-adapted (M = 2.21, SD = 3.57) UA trials. There was no main effect of
Group, F(1, 56) = 0.11, p = 0.743, η2p < 0.01, BFincl = 0.25, and no Group * Adapted Direction
interaction, F(1, 56) < 0.01, p = .953, η2p < 0.01, BFincl = 0.25. This indicated that the size of
the cumulative VAE, i.e. the difference in mean constant error between leftward- and
rightward-adapted UA trials, did not differ between patients (M = 3.70, SD = 4.28) and
healthy controls (M = 3.62, SD = 5.0). Two separate one-tailed t-Tests confirmed that each
group independently showed a significant cumulative VAE, both p < .001 (see Figure 11 left
panel for the mean and distribution of cumulative VAE size per group).
3.1.4 Immediate VAE
A mixed ANOVA on the mean constant error in UA trials with a preceding leftward-
vs. rightward-adaptation AV trial revealed a highly significant main effect of Direction of
Preceding AV Adaptation, F(1, 56) = 43.21, p < .001, η2p = 0.44, BFincl > 1000, indicating that
the mean constant error differed between UA trials with an preceding leftward-adaptation (M
= -0.28, SD = 3.74) vs. a preceding rightward-adaptation (M = 1.04, SD = 3.75) AV trial.
There was no main effect of Group, F(1, 56) = 0.11, p = 0.743, η2p < 0.01, BFincl = 0.52, and
no Group * Direction of Preceding AV Adaptation interaction, F(1, 56) = 0.28, p = 0.597, η2p =
0.01, BFincl = 0.48. This indicated that the size of the immediate VAE, i.e. the difference in
mean constant error between UA trials with a preceding leftward- vs. rightward-adaptation AV
trial, did not differ between patients (M = 1.43, SD = 1.37) and healthy controls (M = 1.22, SD
= 1.65). Two separate one-tailed t-Tests confirmed that each group independently showed a
significant immediate VEA, both p < .001 (see Figure 11 right panel for the mean and
distribution of immediate VAE size per group).
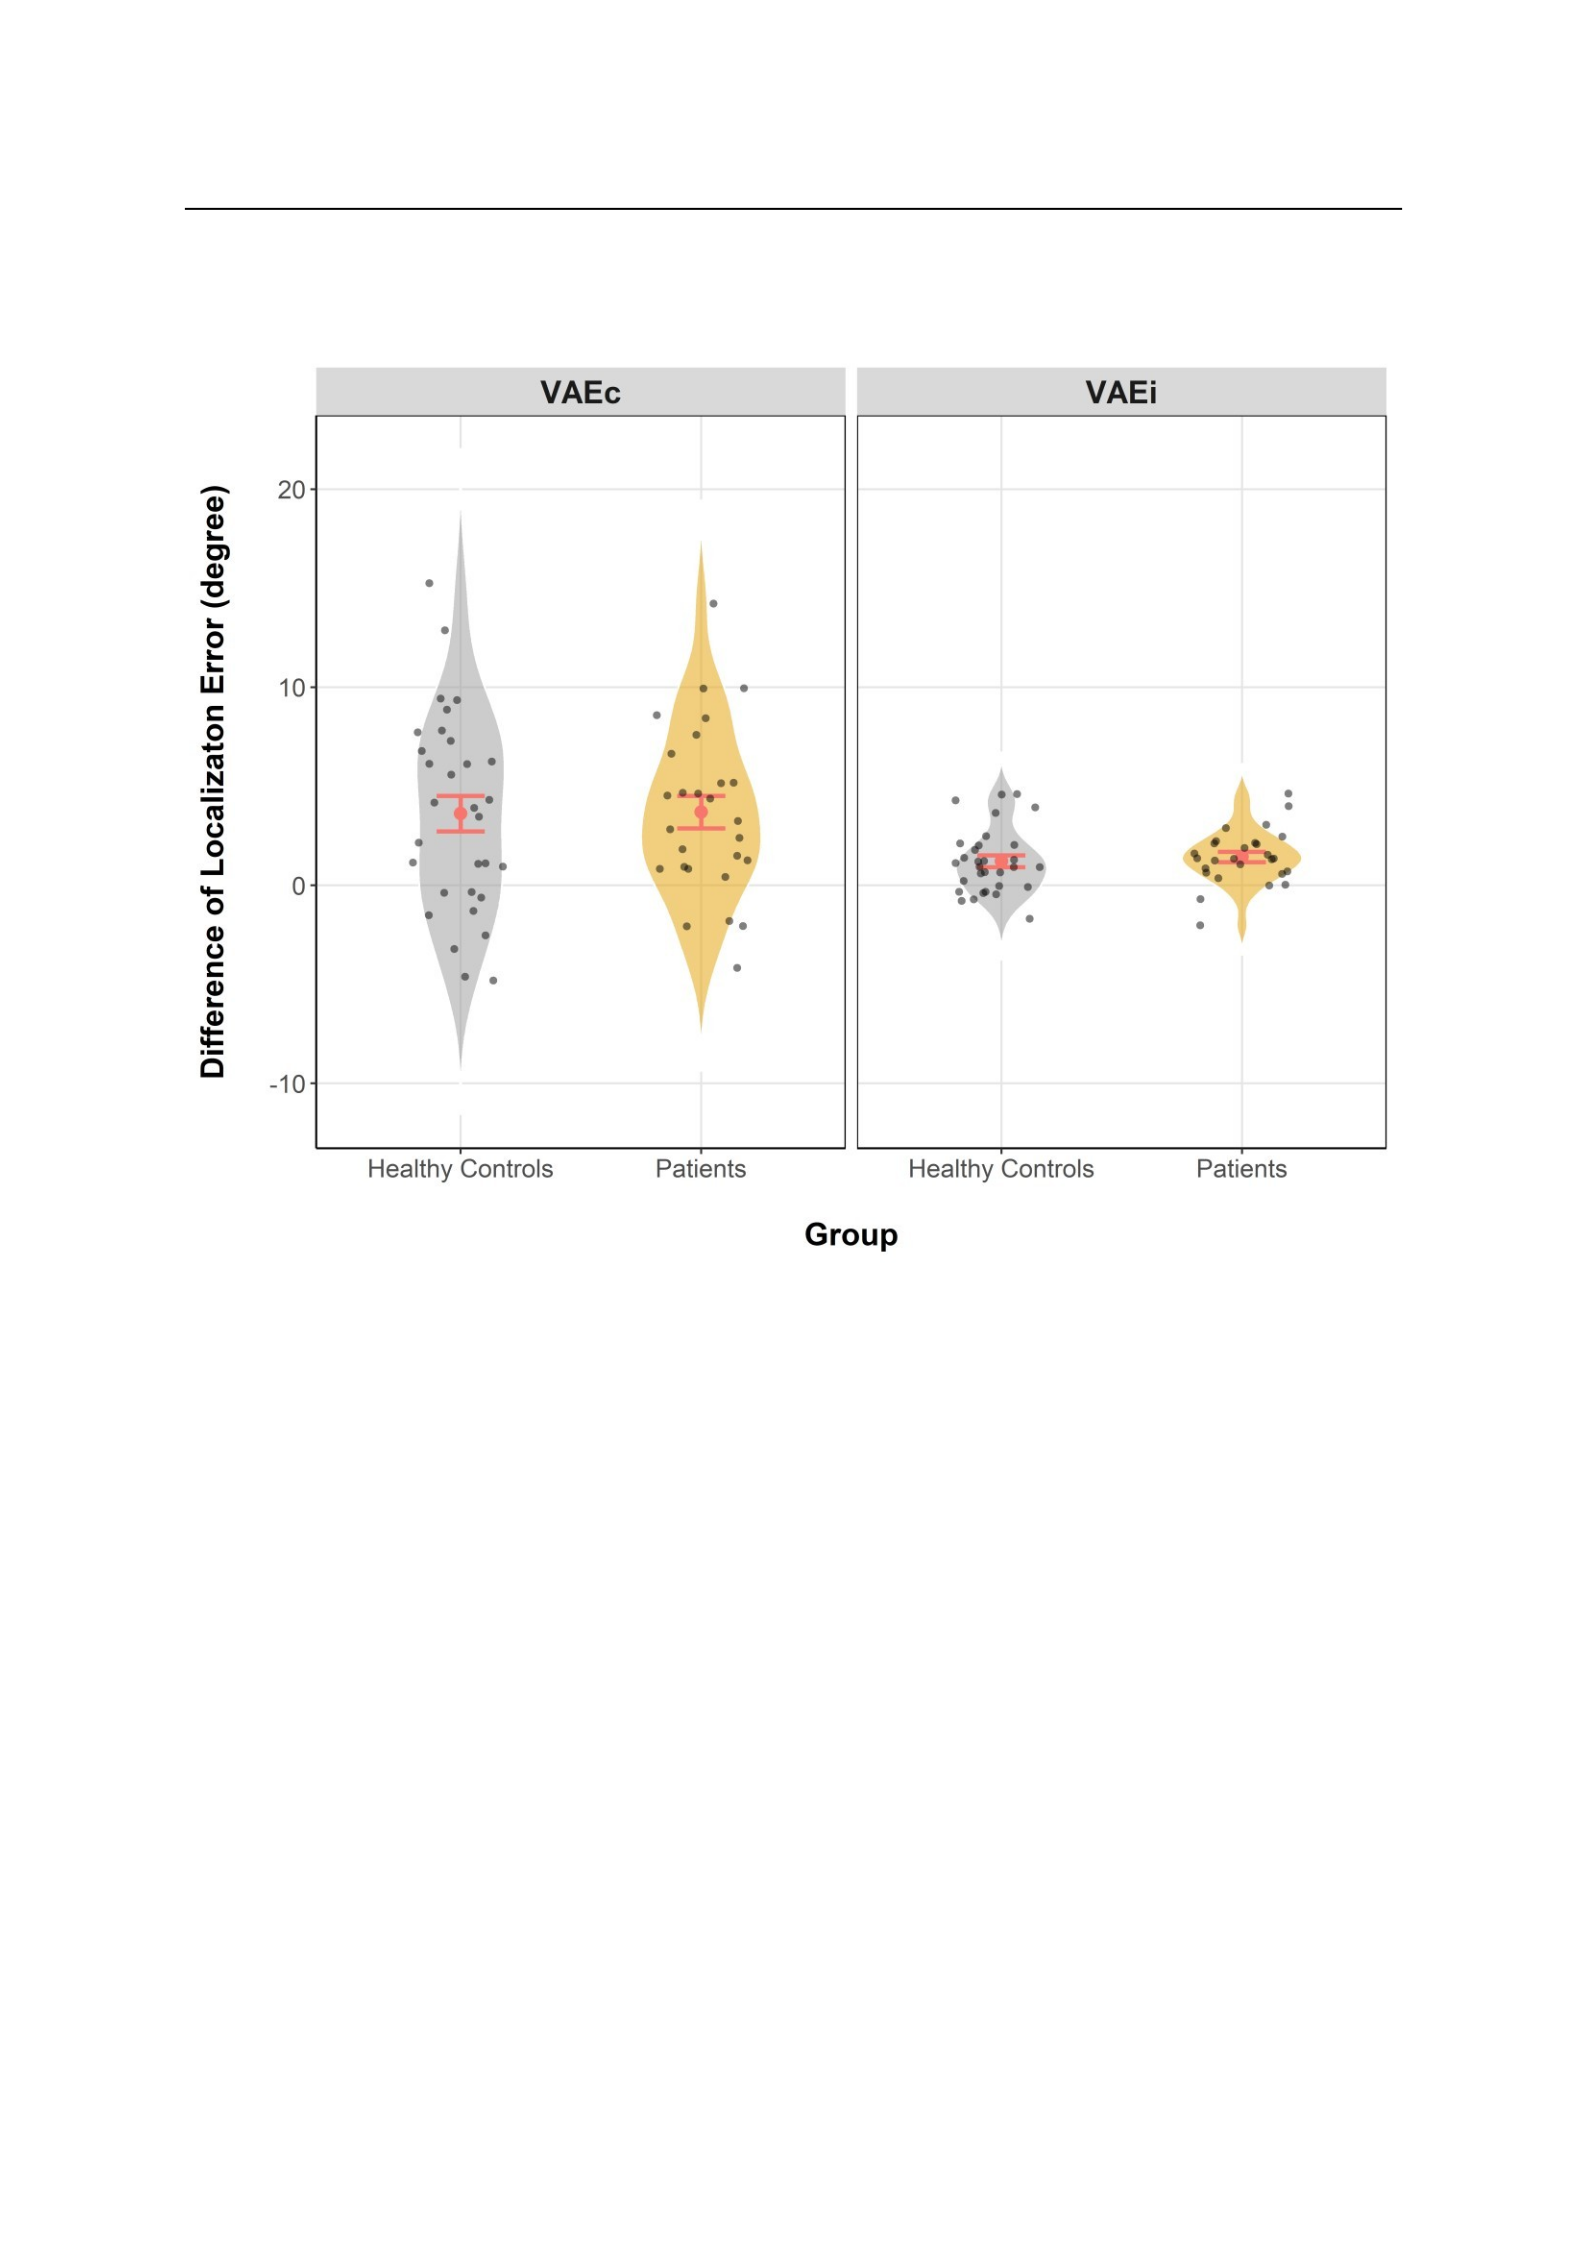
125
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Figure 11
Mean & Distribution of Cumulative and Immediate Ventriloquist Aftereffect Size
Notes. nHC = 31; nPAT = 27. VAEc = cumulative ventriloquist aftereffect; VAEi = immediate ventriloquist
aftereffect. The left panel shows the difference in constant error between the leftward- and rightward-adapted
sound frequency in unimodal auditory trials. The right panel shows the difference in constant error between
unimodal auditory trials preceded by an audiovisual trial with leftward- vs. rightward-adaptation. Per group, the
mean, error bars denoting the SEM, the value distributions as well as the individual data points are depicted for
both the cumulative and immediate VAE.
3.1.5 Accumulation of the Immediate VAE
Consecutive Preceding Trials with Same Frequency. A mixed ANOVA for the
accumulation of the immediate VAE in UA trials preceded by AV trials with the same
frequency revealed a significant main effect of Consecutive Trial Number, F(3, 168) = 2.90, p
= .037, η2p = 0.5, BFincl = 0.53. However, Bonferroni-corrected post-hoc t-Tests for pairwise
comparisons did not reveal any significant difference in immediate VAE size between UA
trials with one, two, three or four consecutive preceding AV same frequency trials, all p > .05.
There was no significant main effect for Group, F(1, 56) = 0.05, p = .832, η2p < 0.01, BFincl =

126
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
0.26, nor a significant Group * Consecutive Trial Number interaction, F(3, 168) = 1.59, p
= .193, η2p = 0.03, BFincl = 0.14 (see Figure 12 for the accumulation of immediate VAE size
over the last one to four adaptation trials).
Consecutive Preceding Trials with Different Frequency. A mixed ANOVA for the
accumulation of the immediate VAE in UA trials preceded by AV trials with the other
frequency revealed a highly significant main effect of Consecutive Trial Number, F(3, 168) =
8.84, p < .001, η2p = 0.14, BFincl = 688.32. Bonferroni-corrected post-hoc t-Tests for pairwise
comparisons revealed a significant difference in immediate VAE size between UA trials with
one (M = 4.14, SD = 5.66) and with three (M = 1.40, SD = 5.45) consecutive preceding AV
different frequency trials, t(57) = 4.45, p < .001, Cohen’s d = 0.49, as well as between UA
trials with one and with four (M = 0.78, SD = 6.34) consecutive preceding AV different
frequency trials, t(57) = 5.08, p < .001, Cohen’s d = 0.56, reflecting that the VAE induced by
the frequency - adaptation direction mapping decreased with increasing numbers of preceding
adaptation trials of the different frequency. All other post-hoc comparisons did not reach
statistical significance, all p > .05. There was no significant main effect for Group, F(1, 56) =
0.31, p = .580, η2p < 0.01, BFincl = 0.28, nor a significant Group * Consecutive Trial Number
interaction, F(3, 168) = 0.99, p = .400, η2p = 0.02, BFincl = 0.15 (see Figure 12 for the
accumulation of immediate VAE size over the last one to four adaptation trials).
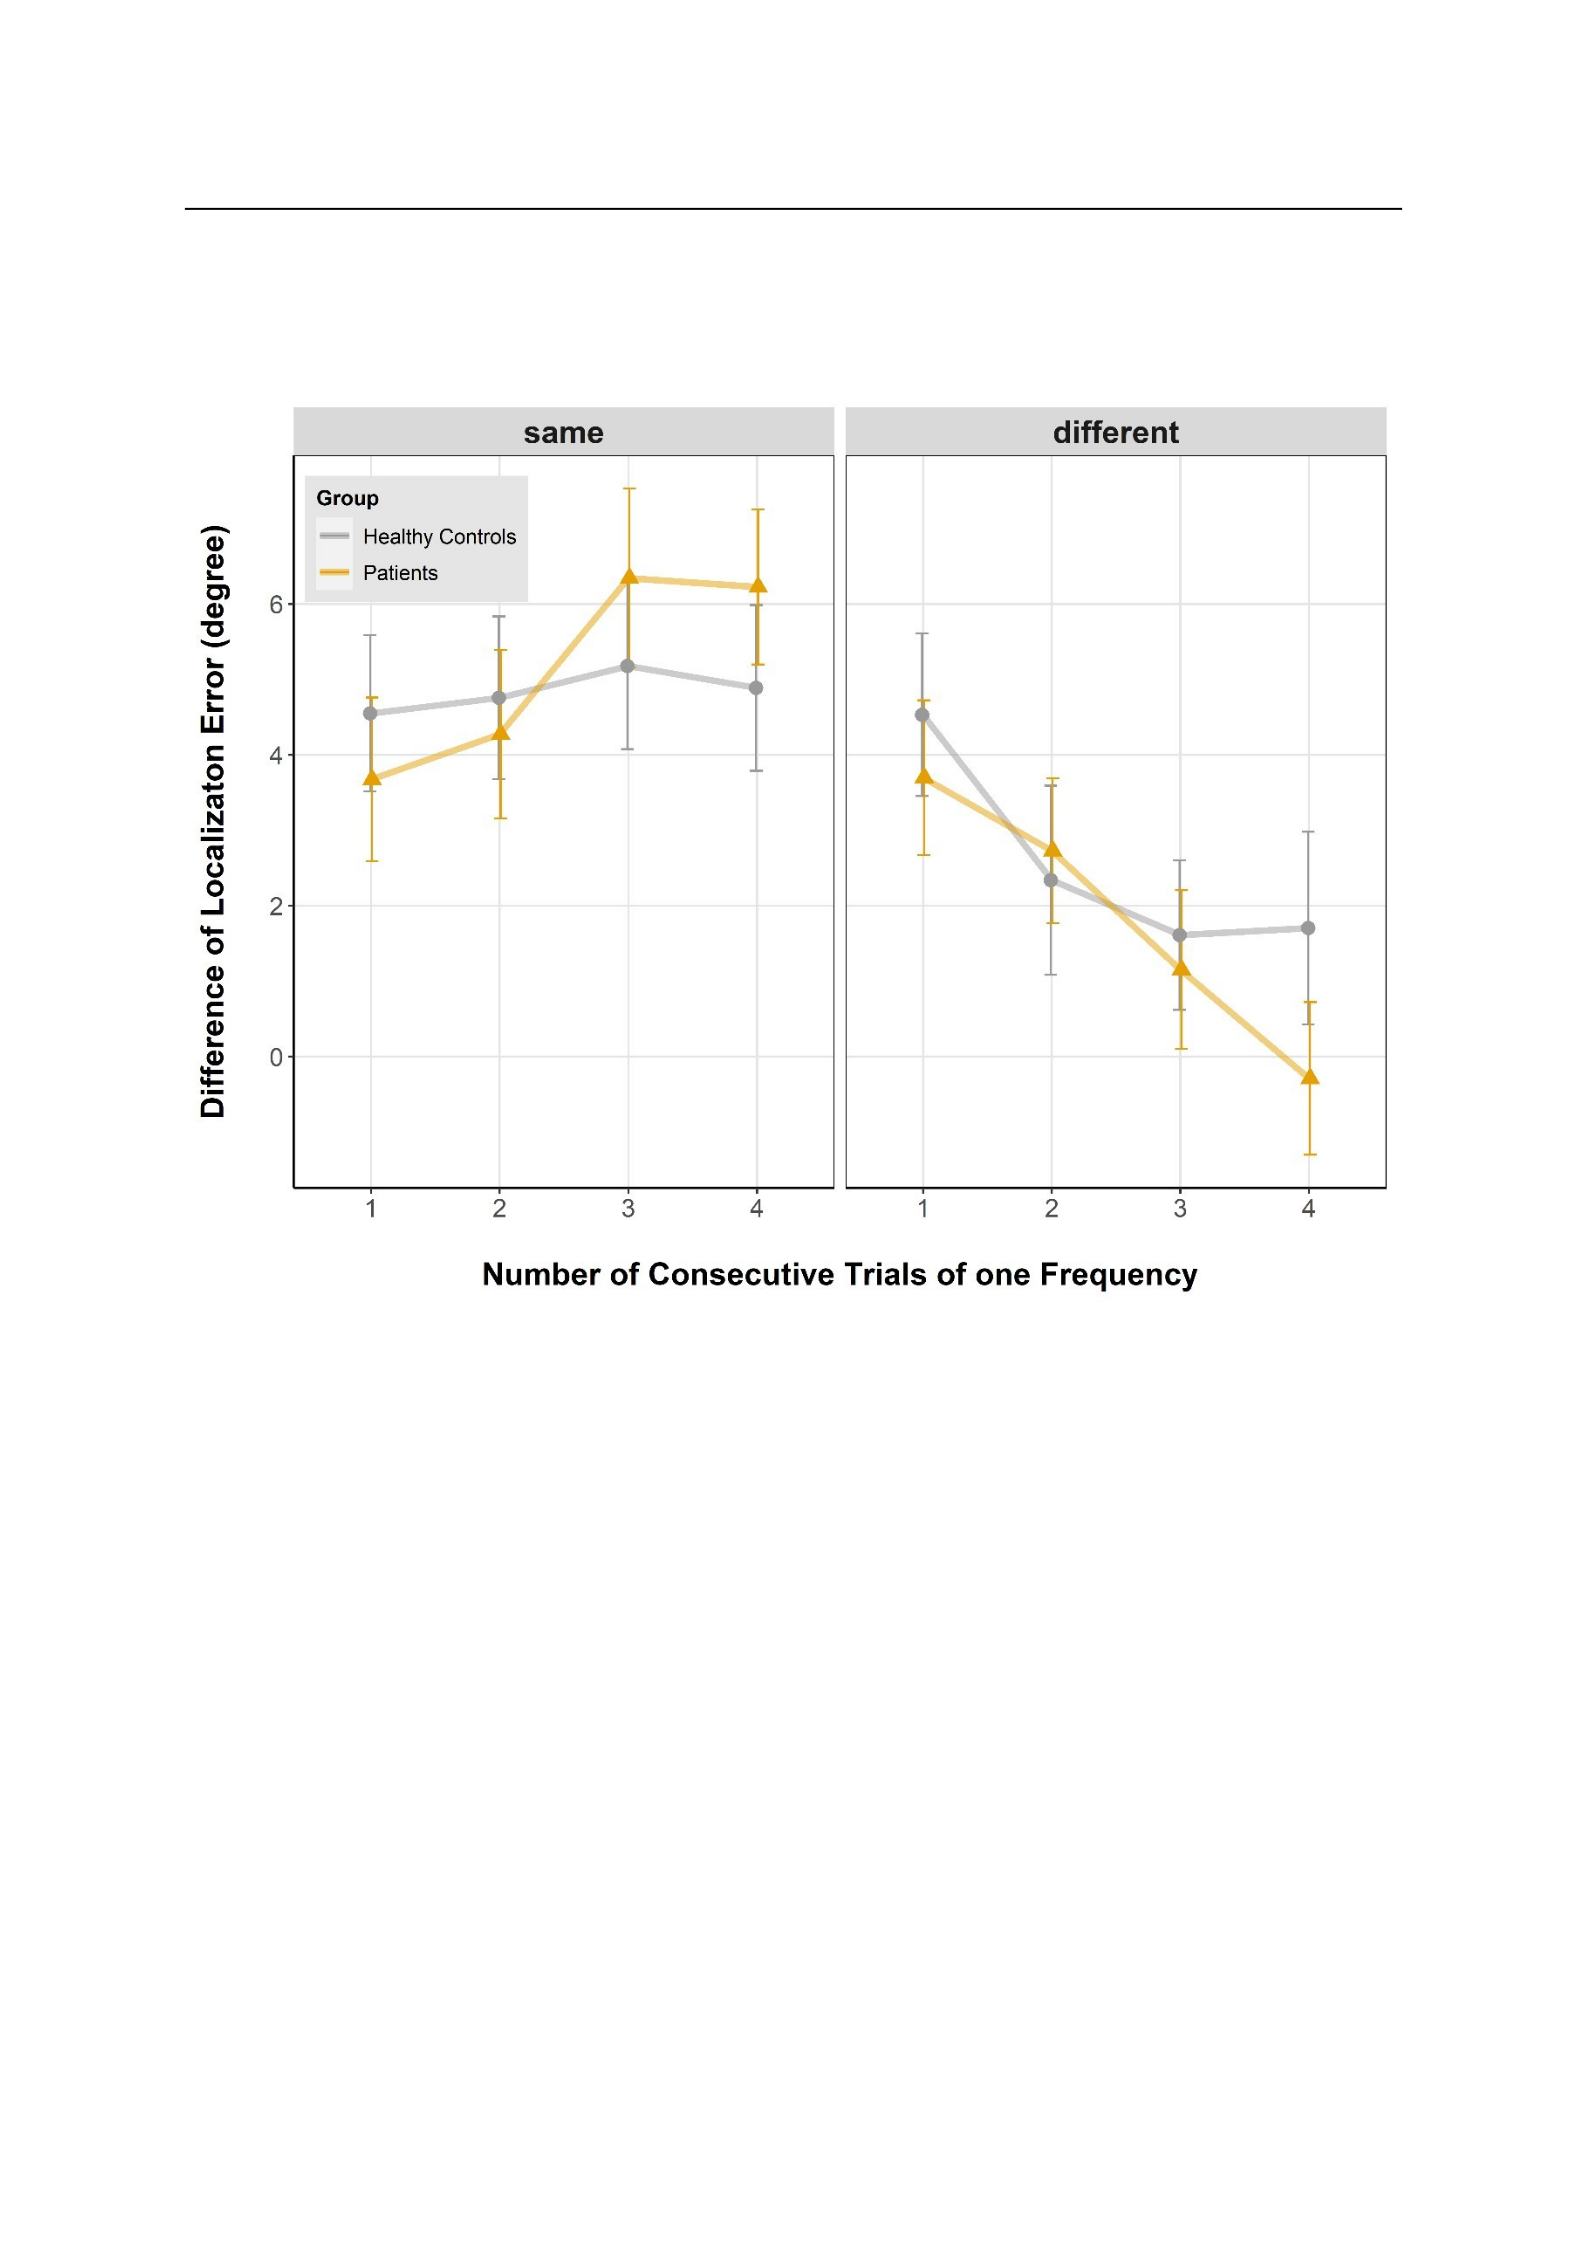
127
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Figure 12
Accumulation of the Immediate Ventriloquist Aftereffect over Consecutive Preceding
Audiovisual Trials with one Frequency
Notes. nHC = 31; nPAT = 27. The left panel shows the difference in constant error between unimodal auditory (UA)
trials preceded by an audiovisual (AV) trial with leftward- vs. rightward-adaptation relative to the number of
consecutive trials with the same frequency as the UA trials. The right panel shows the difference in constant
error between UA trials preceded by an AV trial with leftward- vs. rightward-adaptation relative to the number of
consecutive trials with the different frequency as the UA trials. Error bars denote the SEM.
3.1.6 Correlations Between VE, Cumulative VAE, and Immediate VAE
The VE showed significant, moderate Spearman rank correlations with both the
cumulative VAE, Spearman’s ρ = .44, p = .003, BF10 = 261.81, and the immediate VAE,
Spearman’s ρ = .36, p = .018, BF10 = 7.56. Cumulative VAE and immediate VAE showed no
significant correlation, Spearman’s ρ = .15, p = .753, BF10 = 0.26. p-values are
Bonferronicorrected (see Table 6 for Spearman rank correlation coefficients ρ. Exploratory
Spearman rank coefficients ρ split by group can be found in Table D.1 and Table D.2 in
Appendix D).

128
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Table 6
Spearman Rank Correlation Coefficients ρ for Associations Between VE, Cumulative VAE,
Immediate VAE and Questionnaire Scores over all Participants
1. 2. 3. 4. 5. 6. 7. 8. 9.
1. VE
2. VAEc
.44**
3. VAEi .36* .15
4. CAPS .21 .18 .14
5. LSHS-E .22 .10 .11 .79***
6. PCL .18 .05 .11 .68*** .66***
7. Pass. Exp. .19 -.06 .12 .67*** .79*** .59***
8. BCSS n.S. .14 -.03 .07 .63*** .63*** .63*** .60***
9. BCSS n.O. .21 .02 -.13 .39* .49*** .55*** .47*** .55***
Notes. N = 58. Spearman rank correlation coefficients ρ > .3 are marked in bold. p-values are
Bonferronicorrected. VE = ventriloquist effect size; VAEc = cumulative ventriloquist aftereffect size; VAEi =
immediate ventriloquist aftereffect size; CAPS = Cardiff Anomalous Perception Scale, total score; LSHS-E =
Launey-Slade Hallucination Scale-Extended, total score; PCL = Paranoia Checklist, total score; Pass. Exp. =
total score in passivity experiences items; BCSS n.S. = Brief Core Schema Scales, negative self subscale; BCSS
n.O. = Brief Core Schema Scales, negative other subscale.
* p < .05, ** p < .01, *** p < .001
3.1.7 Exploratory Analysis of Non-Merged Data
AV Trials. An exploratory mixed ANOVA with the between-factors Group (patients
vs. healthy controls) and Adaptation Direction (750R/3000L vs. 750L/3000R) and the
withinfactor Frequency (750Hz vs. 3000Hz) on mean constant error in AV trials revealed a
highly significant main effect of Frequency, F(1, 54) = 27.68, p < .001, η2p = 0.34, BFincl >
1000, and a significant main effect of Adaptation Direction, F(1, 54) = 5.95, p = .018, η2p =
0.10, BFincl > 1000. Crucially, the Frequency * Adaptation Direction interaction was highly
significant, F(1, 54) = 238.38, p < .001, η2p = 0.82, BFincl > 1000, indicating a bias in sound
localization due to the concurrently presented visual stimulus consistent with the respective
AV spatial mismatch, i.e. reflecting the VE. The main effect of Group only showed a non-
significant trend, F(1, 54) = 3.80, p = .056, η2p = .07, BFincl = 0.35, indicating that patients (M
= 2.75, SD = 2.93) and healthy controls (M = 1.33, SD = 2.72) displayed a non-significant
trend towards localization error bias differences during AV trials. All other effects did not
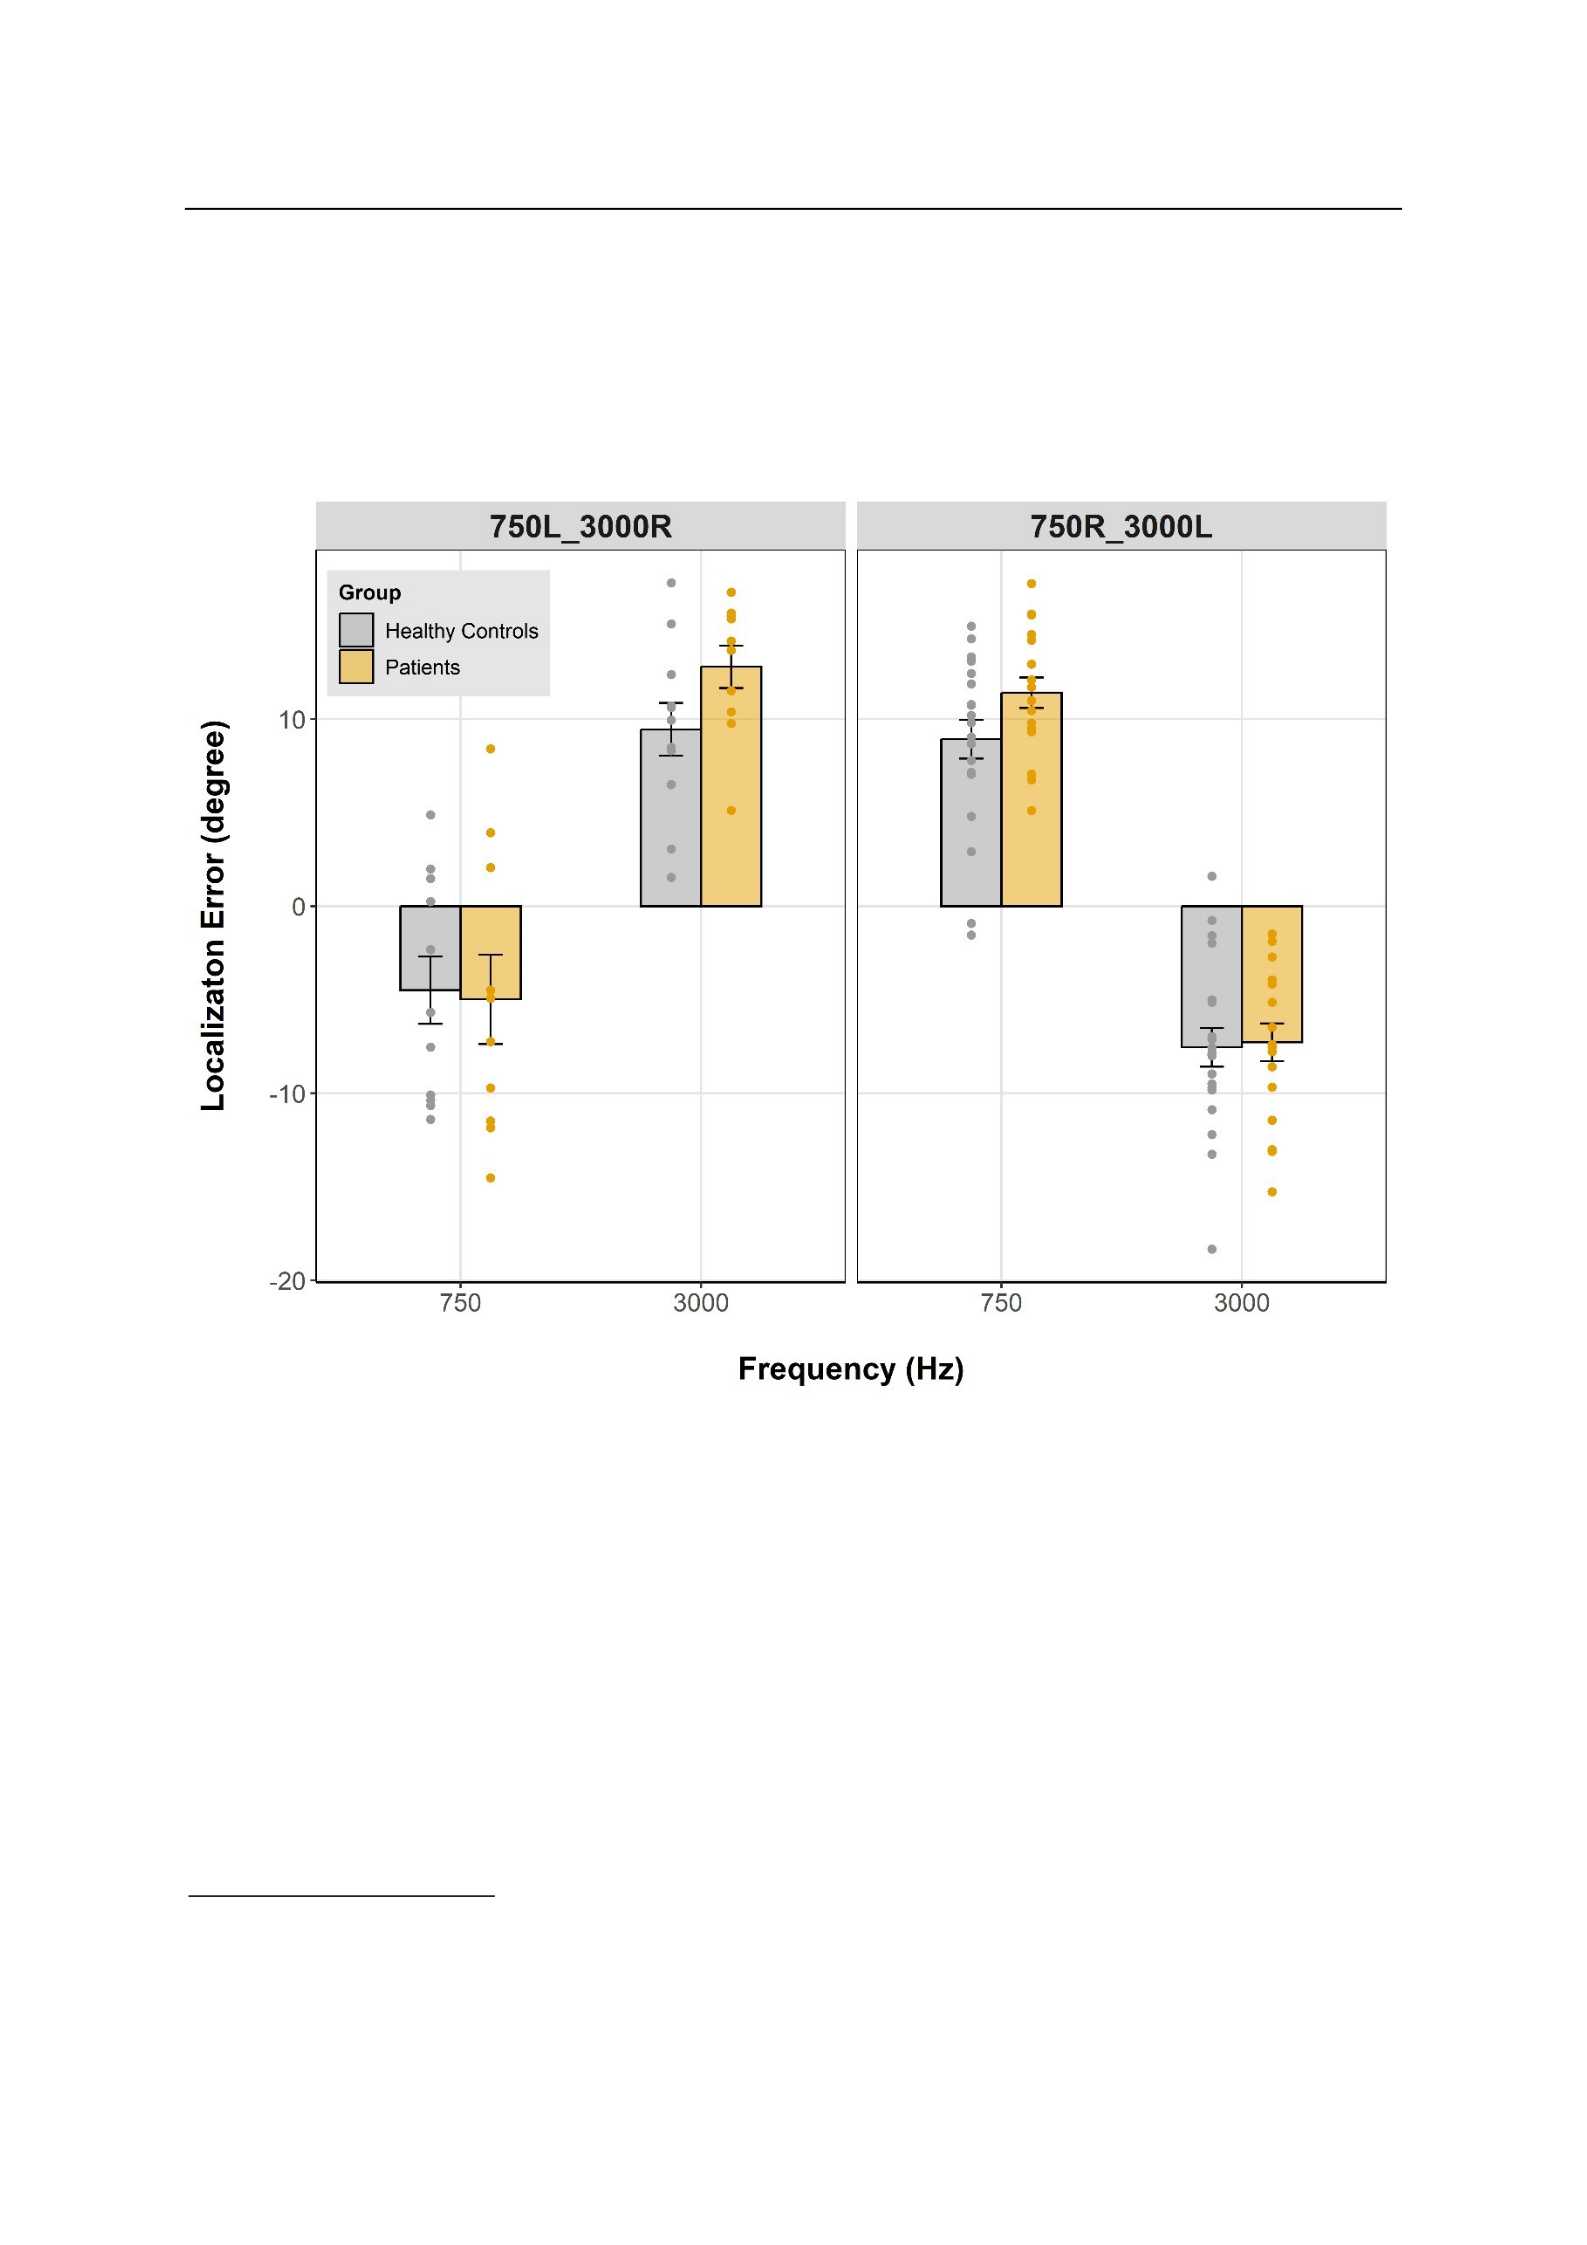
129
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
reach statistical significance, all p > .05 and all BFincl < 1 (see Figure 13 for localization
responses in AV trials).
Figure 13
Localization Error in Audiovisual Trials
Notes. nHC = 31; nPAT = 27. The mean constant error in audiovisual trials is depicted per sound frequency (750Hz
& 3000 Hz) and group for the non-merged data, i.e. separately for both adaptation directions (750 Hz
leftward/3000 Hz rightward & 750 Hz rightward/3000 Hz leftward). Depicted are the mean, error bars denoting
the SEM, and the individual data points.
UA Trials.9 An exploratory mixed ANOVA with the between-factors Group (patients
vs. healthy controls) and Adaptation Direction (750R/3000L vs. 750L/3000R) and the
withinfactors Frequency (750Hz vs. 3000Hz) and Frequency of prior adaptation trail (same
vs.
9 The Group * Adaptation Direction * Frequency * Frequency on of prior adaptation trial Bayesian mixed
ANOVA unexpectedly reported BFincl > 1000 for some factors, which were non-significant in the frequentist
analysis, all p > .05. We speculate that the current JASP version 0.16.4 is not yet built for a Bayesian ANOVA with
two between- and two within-factors, possibly leading to computational errors due to the high amount of resulting
candidate models. We assume that BFincl are erroneous and therefore do not report the results of above mentioned
Bayesian mixed ANOVA.

130
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
different) on mean constant errors in UA auditory trials revealed a highly significant
Frequency * Adaptation Direction interaction, F(1, 54) = 33.76, p < .001, η2p = 0.38,
indicating a bias in sound localization in UA trials induced by the respective AV spatial
mismatch in AV adaptation trials, i.e. reflecting the cumulative VAE. There further was a
highly significant Frequency * Adaptation Direction * Frequency of prior adaptation trial
interaction, F(1, 54) = 40.26, p < .001, η2p = 0.43, indicating that the similarity in frequency
and therefore the direction of the AV spatial mismatch of the previous adaptation trial in the
immediate stimulus history had an impact on sound localization responses in UA trials, i.e.
reflecting the immediate VAE. There also was a significant Group * Adaptation Direction *
Frequency of prior adaptation trial interaction, F(1, 54) = 4.64, p = .036, η2p = 0.08. Two
follow-up ANOVAs separately for each group revealed that the Adaptation Direction *
Frequency of prior adaptation trial interaction did not remain significant for either group
(healthy controls p = .339; patients p = .071). The main effect of Group only showed a
nonsignificant trend, F(1, 54) = 3.51, p = .066, η2p = .06, implying that patients (M = 2.95, SD
= 2.95) and healthy controls (M = 1.50, SD = 2.86) displayed a non-significant tendency
towards localization error bias differences during UA trials. All other effects did not reach
statistical significance, all p > .05 (see Figure 14 for localization responses in UA trials and
Figure 15 for localization responses in UA trials split by same vs. different frequency of prior
adaptation trial).
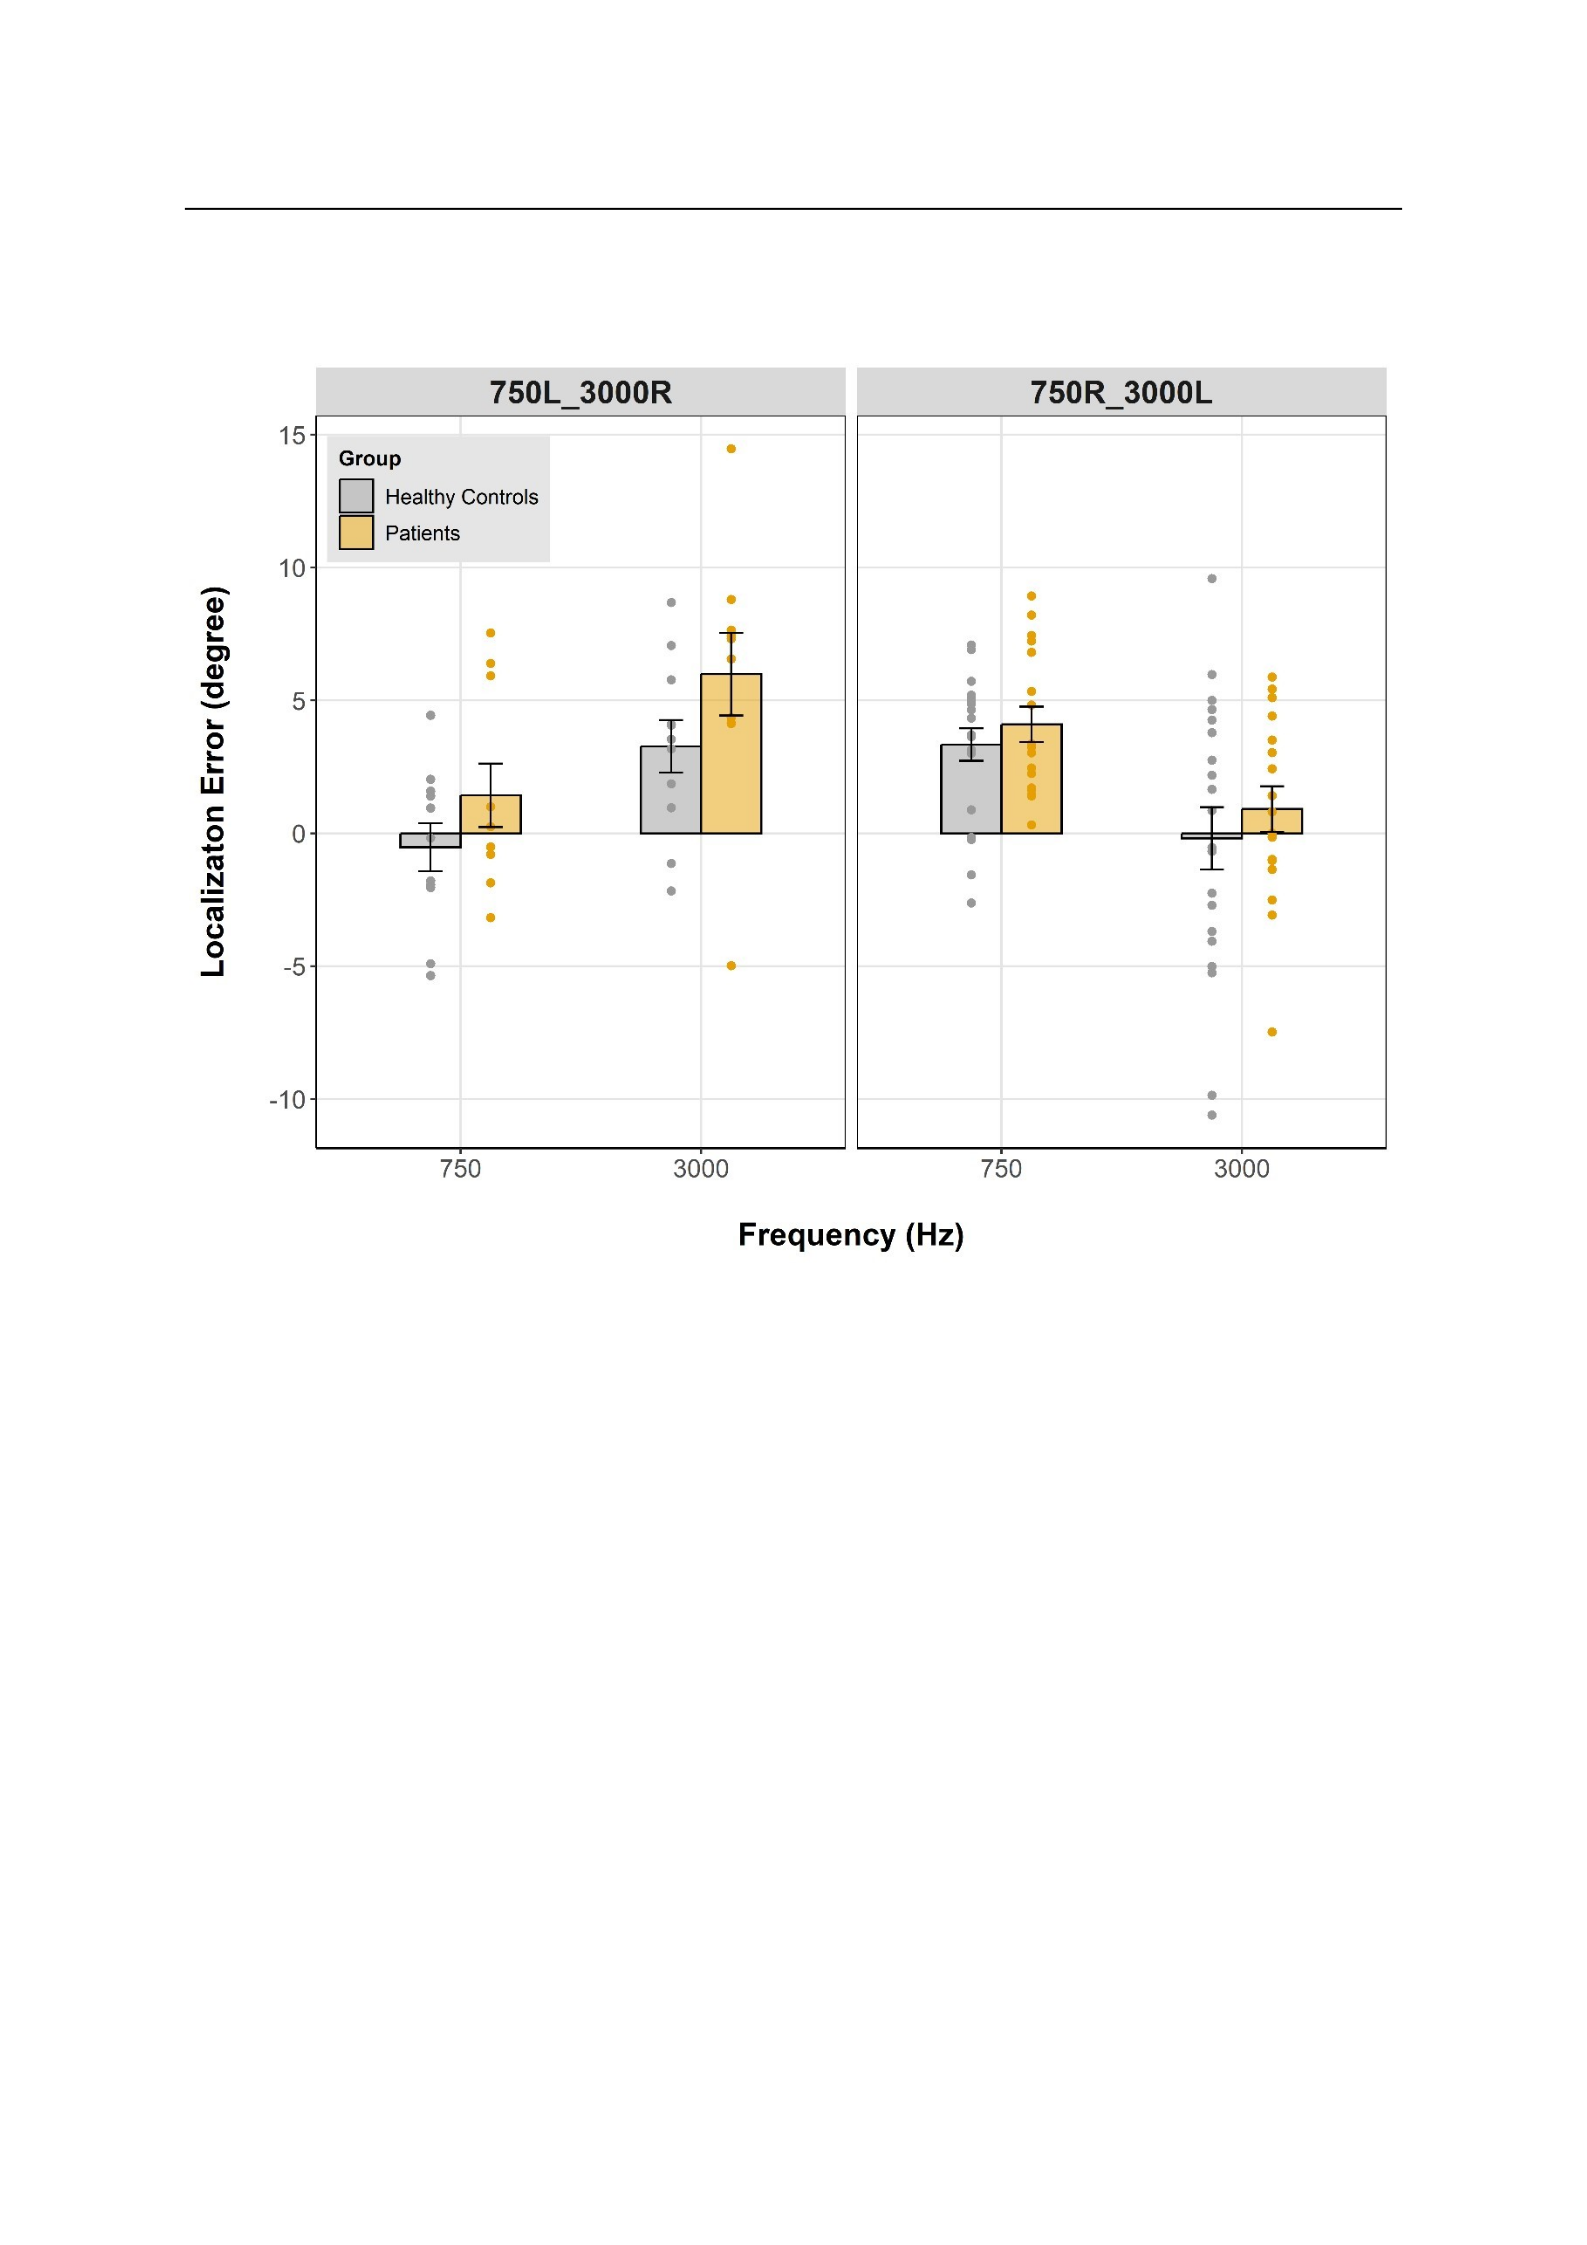
131
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Figure 14
Localization Error in Unimodal Auditory Trials
Notes. nHC = 31; nPAT = 27. The mean constant error in unimodal auditory trials is depicted per sound frequency
(750Hz & 3000 Hz) and group for the non-merged data, i.e. separately for both adaptation directions (750 Hz
leftward/3000 Hz rightward & 750 Hz rightward/3000 Hz leftward). Depicted are the mean, error bars denoting
the SEM, and the individual data points.
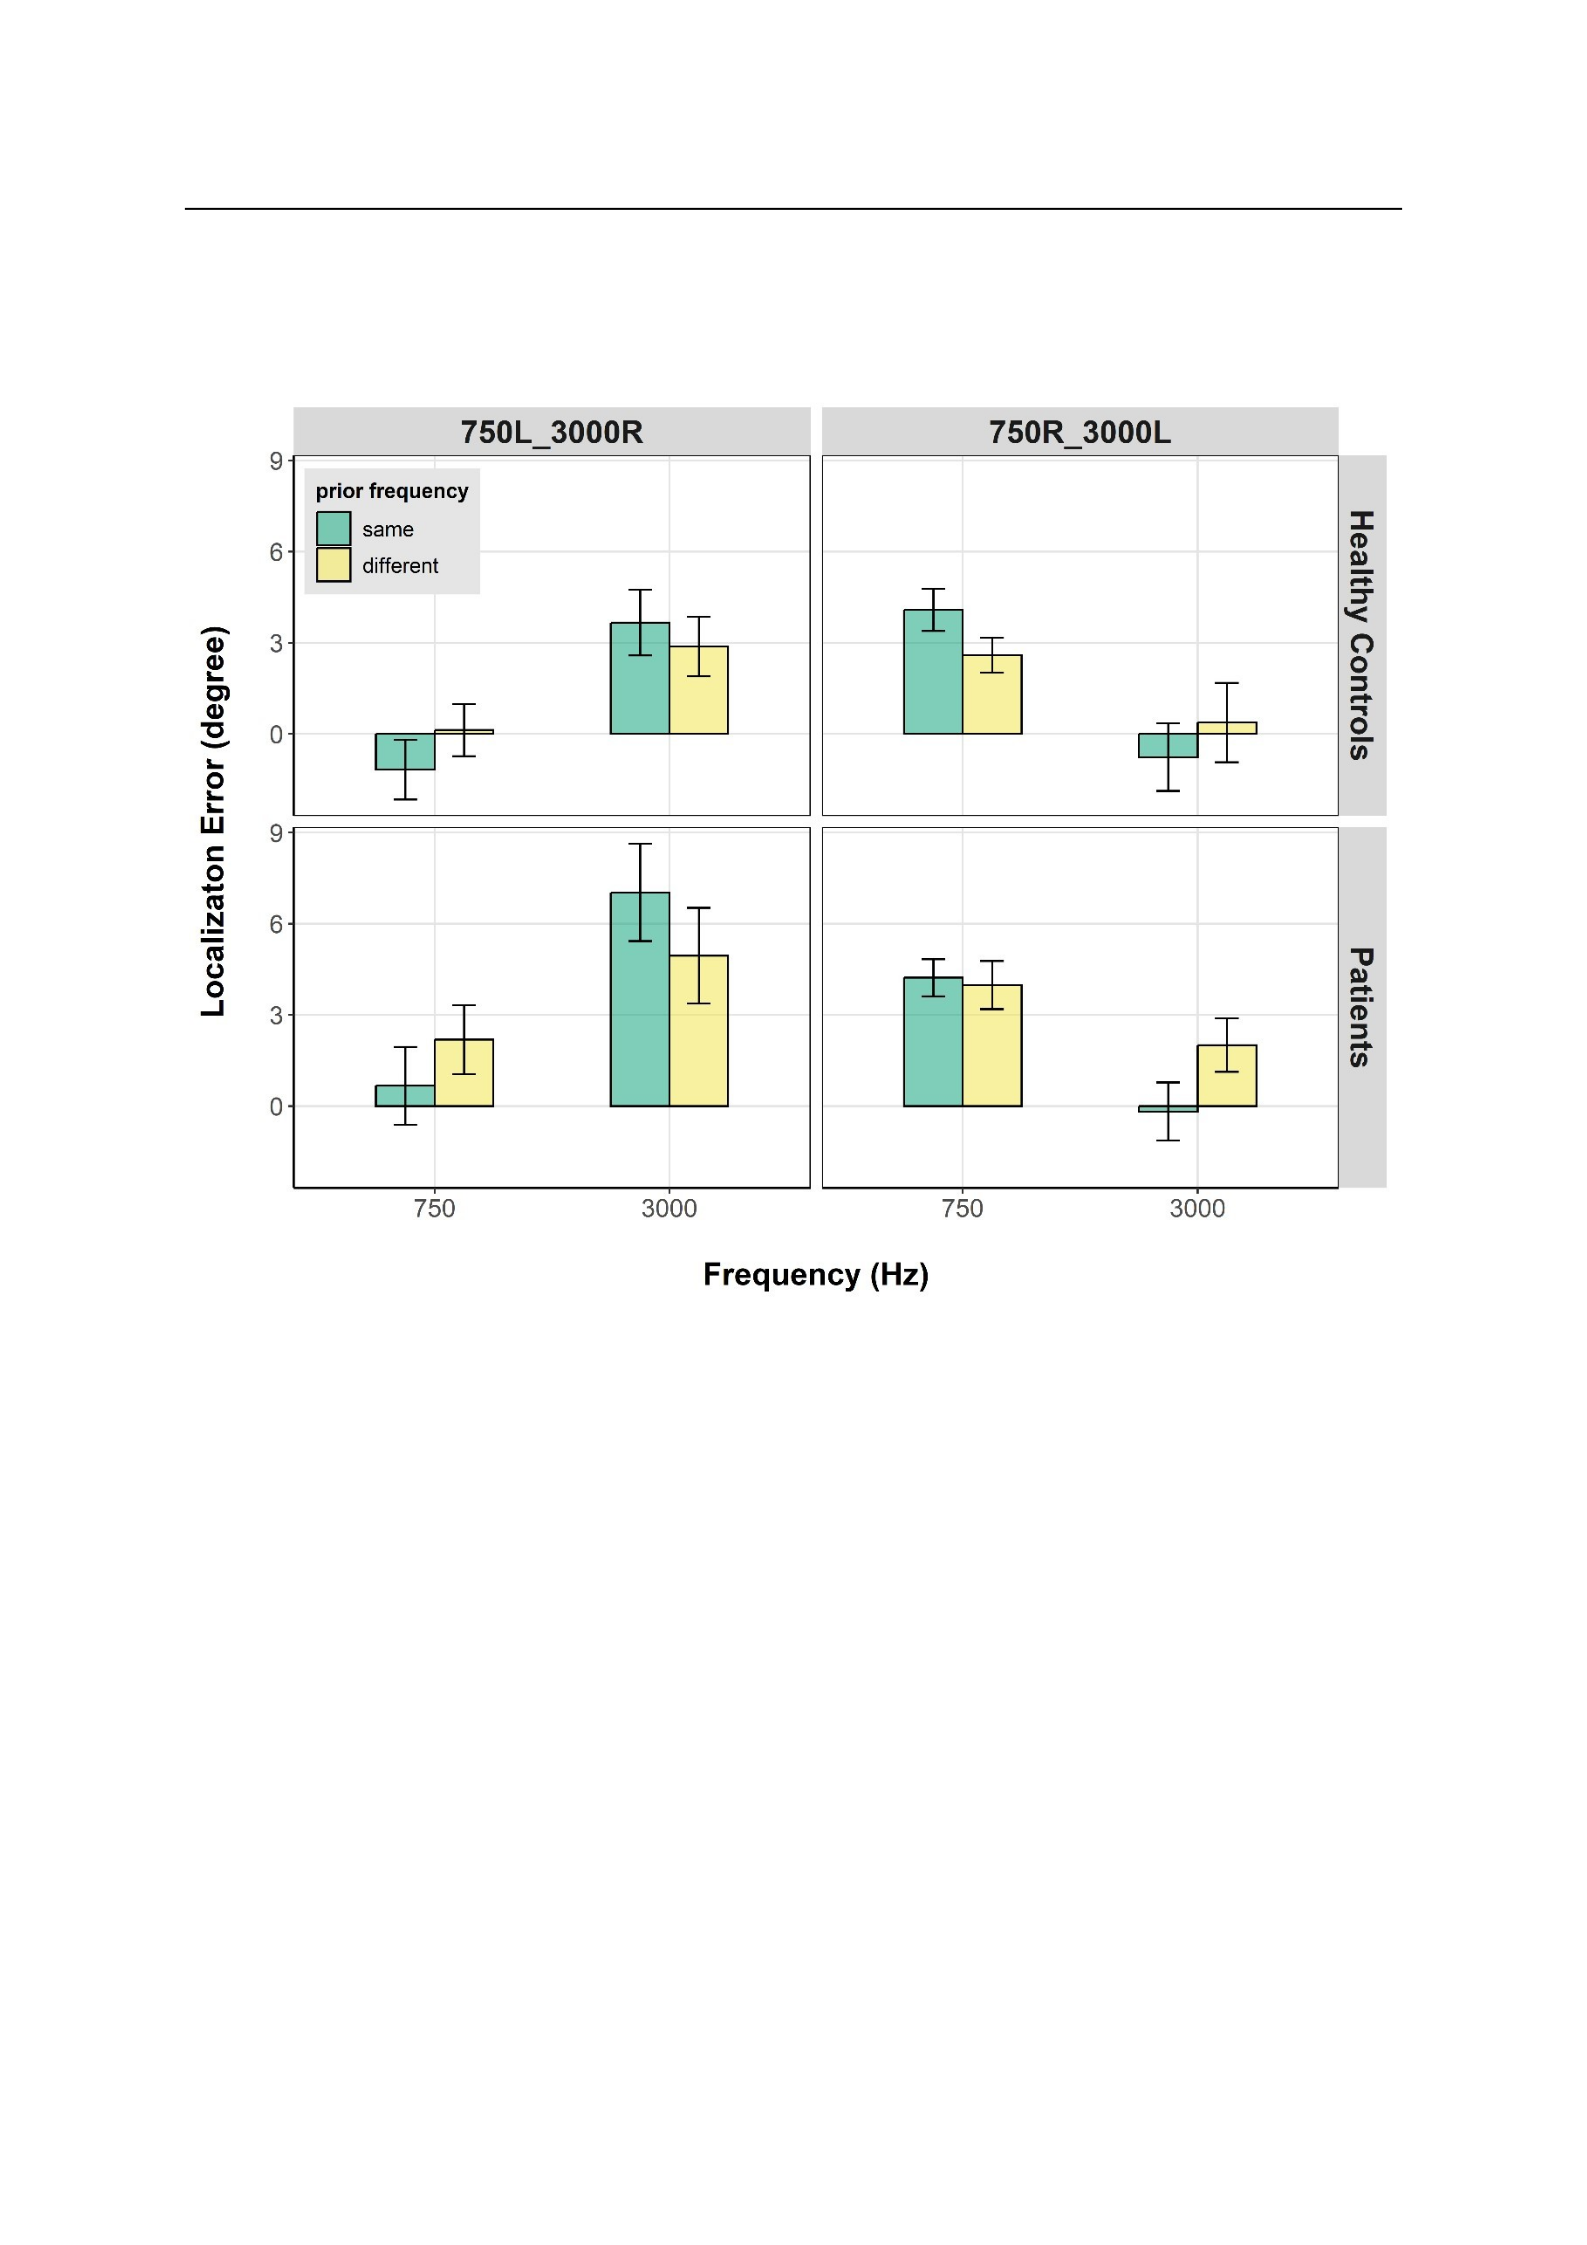
132
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Figure 15
Localization Error in Unimodal Auditory Trials Following an Audiovisual Trial with the Same
or Different Frequency
Notes. nHC = 31; nPAT = 27. The mean constant error in unimodal auditory trials following an audiovisual trial of
the same or different frequency is depicted per group and per sound frequency (750Hz & 3000 Hz) for the
nonmerged data, i.e. separately for both adaptation directions (750 Hz leftward/3000 Hz rightward & 750 Hz
rightward/3000 Hz leftward). Depicted are the mean and error bars denoting the SEM.
3.2 Control Variables and Questionnaire Data
3.2.1 Control Tests for Attention, Processing Speed, and Vigilance
TMT. Patients (M = 31.05, SD = 11.06) and healthy controls (M = 26.13, SD = 9.11)
showed a non-significant trend towards TMT-A completion time (in seconds) differences,
t(50.52) = 1.83, p = .073, Cohen’s d = 0.49, BF10 = 1.1. Groups differed significantly in
TMTB completion time (in seconds), with patients needing more time to complete the test (M
= 84.84, SD = 40.51) compared to healthy controls (M = 56.37, SD = 20.44), t(37.23) = 3.3, p
= .002, Cohen’s d = 0.91, BF10 = 28.87.

133
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
CPT-IP. A mixed ANOVA for CPT-IP d’ scores revealed a significant main effect of
Group, F(1, 112) = 9.03, p = .004, η2p = 0.14, BFincl = 10.46, indicating that patients showed
overall lower d’ scores (M = 2.32, SD = 1.15) compared to healthy controls (M = 2.81, SD =
1.14). Further, there was a highly significant main effect of Digit Load, F(2, 112) = 252.38, p
< .001, η2p = 0.82, BFincl > 1000. Bonferroni-corrected post-hoc t-tests revealed that d’ scores
were larger in the 2-digit condition (M = 3.55, SD = 0.65) compared to both the 3-digit
condition (M = 2.74, SD = 0.88), t(57) = 9.23, p < .001, and the 4-digit condition (M = 1.46,
SD = 0.81), t(57) = 22.31, p < .001, and larger in the 3-digit condition compared to the 4-digit
condition, t(57) = 13.09, p < .001. There was no significant Group * Digit condition
interaction, F(2, 112) = 2.06, p = .132, η2p = 0.04, BFincl = 1.79.
Association Between Experimental Data and Control Variables. VE, cumulative
VAE, and immediate VAE data did not show any significant Spearman rank correlations with
TMT and CPT-IP data, all Spearman’s ρ ≤ .31 and all p > .05 (see Table D.3 in Appendix D
for Spearman rank correlation coefficients ρ).
3.2.2 Questionnaires
CAPS. Groups differed significantly in CAPS scores, with patients reporting
significantly higher number of aberrant perceptual experiences (M = 9.9, SD = 6.7) compared
to healthy controls (M = 2.2, SD = 2.4), t(31.85) = 5.95, p < .001, Cohen’s d = 1.55, BF10 >
1000.
LSHS. Groups differed significantly in LSHS-E total scores, with patients reporting
significantly higher occurrence of hallucinations (M = 22.3, SD = 11.3) compared to healthy
controls (M = 4.4, SD = 4.4), t(32.86) = 7.76, p < .001, Cohen’s d = 2.15, BF10 > 1000.
PCL. Groups differed significantly in PCL total scores, with patients reporting
significantly higher levels of paranoia (M = 81.7, SD = 56.3) compared to healthy controls (M
= 21.3, SD = 18.7), t(30.98) = 5.32, p < .001, Cohen’s d = 1.48, BF10 > 1000.
Passivity Experiences. Groups differed significantly in passivity experiences scores,
with patients reporting significantly higher occurrence of passivity experiences (M = 5.5, SD =
4.4) compared to healthy controls (M = 0.3, SD = 0.5), t(26.62) = 6.19, p < .001, Cohen’s d =
1.75, BF10 > 1000.

134
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
BCSS. Groups differed significantly in BCSS negative self scores, with patients
reporting significantly more negative beliefs about the self (M = 6.9, SD = 4.9) compared to
healthy controls (M = 2.0, SD = 2.1), t(33.96) = 4.91, p < .001, Cohen’s d = 1.35, BF10 = 610.
Further, groups differed significantly in BCSS negative other scores, with patients reporting
significantly more negative beliefs about other people (M = 7.9, SD = 6.1) compared to
healthy controls (M = 3.3, SD = 3.9), t(42.58) = 3.35, p = .002, Cohen’s d = 0.91, BF10 =
29.91.
Correlations Between Questionnaire Scores. The majority of Spearman rank
correlations between CAPS, LSHS-E, PCL, passivity experiences and BCSS negative
subscales was highly significant, all Spearman’s ρ > .40, all p < .001, all BF10 > 15 10, except
for the correlation between CAPS and the BCSS negative other subscale, Spearman’s ρ = .39,
being significant at p = .03, BF10 = 14.71. p-values are Bonferroni-corrected (see Table 6 for
Spearman rank coefficients ρ. Exploratory Spearman rank coefficients ρ split by group can be
found in Table D.1 and Table D.2 in Appendix D).
3.3 Correlations Between Experimental Data and Questionnaire Scores
There were no significant Spearman rank correlations between VE, cumulative VAE as
well as immediate VAE and questionnaire data, all Spearman’s ρ < .3, all p > .05, all BF10 <
1. p-values are Bonferroni-corrected (see Table 6 for Spearman rank coefficients ρ.
Exploratory Spearman rank coefficients ρ split by group can be found in Table D.1 and Table
D.2 in Appendix D).
4 Discussion
In this study, we investigated spatial MSI and crossmodal spatial recalibration in
psychosis. Only few published studies examined spatial MSI in psychosis with their results
suggesting intact spatial MSI (de Gelder et al., 2003; Noel et al., 2020; Stephen et al., 2013;
Stone et al., 2011, 2014). Previous studies on spatial recalibration in psychosis exclusively
focused on sensorimotor processes (e.g. Bartolomeo et al., 2020; Ferri et al., 2016; Rösler et
al., 2015) and to our knowledge no study investigated crossmodal, i.e. sensory-sensory spatial
recalibration in psychosis. Thus, we aimed to replicate earlier findings on intact spatial MSI in
10 The majority of BF10 was > 1000, with following exceptions: LSHS ~ BCSS negative other, BF10 = 289.61,
passivity experiences ~ BCSS negative self, BF10 = 207.42, and passivity experiences ~ BCSS negative other, BF10
= 17.08.

135
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
psychosis (de Gelder et al., 2003; Noel et al., 2020; Stephen et al., 2013; Stone et al., 2011,
2014) and extend findings on spatial recalibration in psychosis to AV stimuli.
Patients with the diagnosis of a psychotic disorder and healthy controls completed a
VE/VAE paradigm with pseudorandomly alternating UA and AV trials (paradigm adopted
from Bruns & Röder, 2015). In each trial, participants localized a sound originating from one
of six different speaker positions by means of a hand pointer. In AV trials, the visual stimulus
was presented with a fixed spatial disparity either to the left or the right of the sound
depending on sound frequency and had to be ignored. Between both groups, we compared the
difference in mean deviance of sound localization responses from the veridical sound position
between leftward- and rightward-adaptation AV trials, reflecting the VE. Further, we
compared the difference in mean deviance of sound localization from the true sound position
between leftward- and rightward-adapted UA trials, reflecting the cumulative VAE, and
between UA trials immediately preceded by a leftward- vs. rightward-adaptation AV trial,
reflecting the immediate VAE.
Our data analysis revealed that patients and controls showed a comparable mean
deviance of sound localization responses from the veridical sound position in all three of the
above described analyses. This indicates similar sizes of the VE, cumulative as well as
immediate VAE in both groups. In the following, these results will be discussed in more detail
with regard to our hypotheses and previous evidence on spatial multisensory processing in
psychosis.
4.1 Hypothesis 1: Psychosis and Spatial Ventriloquism
Our first aim was to replicate previous findings of an intact spatial VE in psychosis (de
Gelder et al., 2003). Thus, we expected patients with the diagnosis of a psychotic disorder to
show a comparable VE size compared to healthy controls.
In line with our hypothesis, the difference in mean constant error during leftward- vs.
rightward-adaptation AV trials did not differ between both groups, reflecting a comparable
size of the VE between patients and healthy controls. Further, both groups individually
showed a significant VE as indicated by group-specific t-tests against zero. Thus, our results
suggest that our patient sample showed intact spatial MSI in our VE paradigm, which
confirmed our hypothesis.

136
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Our results are consistent with an earlier study by de Gelder et al. (2003), who
observed an intact VE using short sequences of AV stimuli. By applying a more typical VE
paradigm with single AV stimulus pairs to avoid within-trial recalibration processes (Bruns,
2019), we were able to replicate the findings of de Gelder et al. (2003) in patients with the
diagnosis of a psychotic disorder. Further, our results are also in line with studies reporting
intact spatial MSI of visuo-tactile stimuli (Noel et al., 2020) and in AV far-near judgements
(Stephen et al., 2013; Stone et al., 2011, 2014) in psychosis. Crucially, unisensory far-near
judgement performance was impaired in auditory and visual only trials, suggesting
crossmodal compensatory mechanisms for unisensory deficits in patients with the diagnosis of
a psychotic disorder (Stephen et al., 2013; Stone et al., 2011, 2014). Alternatively, this could
reflect a consequence of greater attentional capture of crossmodal compared to unimodal
stimuli, which might improve sensory processing (Tseng et al., 2015).
Importantly, although previous studies on AV far-near judgements in psychosis did not
observe multisensory behavioral impairments, these studies reported structural and
neurophysiological differences between patients with the diagnosis of a psychotic disorder
and healthy controls (Stephen et al., 2013; Stone et al., 2011, 2014). By using a joint MEG
and DTI analysis strategy, Stephen et al. (2013) identified neurophysiological and structural
alterations in visual processing pathways in patients compared to controls, such as reduced
occipital MEG amplitude in response to visual stimulation and lower fractional anisotropy in
parietal regions, suggesting visual processing impairments in psychosis. These alterations
were associated with overall RT and measures of cognitive functioning, but not however with
multisensory performance (Stephen et al., 2013). Stone et al. (2014) reported altered
gammaband oscillations in frontal regions as well as in visual and auditory cortices during
unimodal and AV processing in patients compared to controls, which however were not
correlated to increased behavioral crossmodal gain in the patient sample. In an earlier study,
Stone et al. (2011) observed group differences between patients with the diagnosis of a
psychotic disorder and healthy controls in a ERP comparison between AV and unimodal trials
over left occipitaltemporal regions, reflecting greater neural crossmodal gain in patients
compared to controls. In sum, structural and neurophysiological changes during an AV far-
near judgement task in psychosis were either not related to behavioral multisensory
performance or reflected greater crossmodal gain and thus mirrored behavioral findings of

137
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
similar multisensory performance between patients and controls (Stephen et al., 2013; Stone
et al., 2011, 2014).
Our findings indicate intact spatial MSI in psychosis in a VE paradigm with simple AV
stimuli. While this is consistent with previous findings suggesting intact spatial MSI in
patients with the diagnosis of a psychotic disorder (de Gelder et al., 2003; Noel et al., 2020;
Stephen et al., 2013; Stone et al., 2011, 2014), previous evidence in the temporal domain
indicated impaired temporal MSI in psychosis (Zhou et al., 2018). These contrasting findings
in the spatial vs. in temporal domain might offer indirect support for Odegaard’s & Shams’
(2016) findings in healthy participants, which suggested that spatial and temporal MSI might
reflect dissociated processes. In sum, our findings suggest that the integration of spatial
crossmodal information might be unimpaired in psychosis, contrary to findings in the
linguistic, emotional (Lin et al., 2020; Tseng et al., 2015), temporal (Zhou et al., 2018) or
sensorimotor domain (Noel, Cascio, et al., 2017). This in turn might offer support for the
proposition of domain-specific rather than global deficits in MSI in psychosis (Tseng et al.,
2015).
4.2 Hypothesis 2: Psychosis and the Spatial VAE
4.2.1 Discussion and Comparison to Previous Evidence
Our second aim was to provide first experimental evidence for crossmodal, i.e.
sensory-sensory spatial recalibration in psychosis. Previous studies on spatial recalibration in
psychosis exclusively examined sensorimotor processes and reported impairments in e.g.
visuomotor learning processes (Bartolomeo et al., 2020; Rösler et al., 2015). We aimed to
extend those findings to the sensory-sensory domain to investigate if impairments of spatial
recalibration in psychosis can also be observed in AV stimuli. We examined both cumulative
and immediate spatial recalibration in psychosis to obtain a more fine-grained picture of
potential alterations in AV spatial recalibration.
The difference in mean constant error during leftward- vs. rightward-adapted UA trials
did not differ between patients and controls, reflecting a similar size of the cumulative VAE in
both groups. Further, patients and controls did also not differ in the difference in mean
constant error during AV trials immediately preceded by a leftward- vs. rightward-adaptation
AV trial, reflecting a comparable size of the immediate VAE in both groups. Further, separate
t-tests against zero confirmed that both groups individually showed a cumulative VAE and

138
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
immediate VAE. This indicates that our sample of patients with the diagnosis of a psychotic
disorder showed intact cumulative and immediate AV spatial recalibration.
Our findings do not support our hypothesis on altered cumulative spatial recalibration
in patients with the diagnosis of a psychotic disorder. This indicates that both our patients and
control subjects were able to recalibrate their auditory cortical maps to repeated exposure to
consistent AV spatial discrepancies (Chen & Vroomen, 2013). In contrast, our results on the
immediate VAE confirm our hypothesis on immediate spatial recalibration in psychosis. This
indicates that both groups were able to rapidly adapt sound localization to AV spatial conflicts.
In light of previous evidence indicating that spatial MSI and immediate spatial recalibration
might be closely related and based on common underlying neural substrates (Bruns et al.,
2022; Park & Kayser, 2019; Rohlf et al., 2020), this finding is consistent with our results on
an intact VE in our patient sample. These results could suggest that the perceptual and
cognitive processes underlying both the VE and the immediate VAE might be relatively
spared in patients with the diagnosis of a psychotic disorder. Crucially, further research aiming
to replicate our findings are needed to investigate this assumption.
Given the lack of evidence on sensory-sensory spatial recalibration in psychosis,
comparing our findings to previous evidence on sensorimotor spatial recalibration might give
hints for contrasting sensory-sensory and sensorimotor processes in psychosis and
understanding their potential respective role in disorder development.
Bartolomeo et al. (2020) administered a prism adaptation paradigm in psychosis and
observed reduced visuomotor recalibration during and after prism application when reaching
for a target in patients with the diagnosis of a psychotic disorder compared to healthy controls.
Importantly, visuomotor recalibration deficits were not related to motor dysfunction and
deficits were not observed during baseline, suggesting a specific impairment in integrating
and recalibrating visual and proprioceptive input (Bartolomeo et al., 2020). Further, Rösler et
al. (2015) observed impaired visuomotor recalibration of eye movements in patients with the
diagnosis of a psychotic disorder in a saccadic remapping paradigm. Crucially, impaired
recalibration was larger in patients with higher severity of psychotic symptoms (Rösler et al.,
2015), which might indicate a possible link between visuomotor recalibration and psychosis.
Deficits in visuomotor recalibration processes in psychosis such as saccadic remapping
impairments might be rooted in deficits in predicting the sensory consequences of own

139
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
behavior (for a review, see Thakkar & Rolfs, 2019). This hypothesis is based on previous
work on corollary discharge, a cognitive process describing how efference copies of motor
commands and sensory input of own actions are integrated in the respective sensory brain
areas, leading to a sense of agency over own actions. By comparing the efference copy and the
sensory input of the action, the brain is able to explain the sensory input and attenuates its
neural signal. It has been discussed that this process enables the brain to monitor own
behaviour, predict its outcome and by this infer if actions were self-induced (Bansal et al.,
2018; Thakkar et al., 2017).
It has been discussed that psychosis might be associated with impaired signaling of
motor command efference copies, in turn leading to overly high salience of the sensory
consequences of own behaviour, such as seeing the movement of one’s hand (Bansal et al.,
2018; Poletti et al., 2019). The impaired attenuation of sensory signals of own actions might
lead to an impaired sense of agency over own actions and it has been found that impairments
in corollary discharge are associated with psychotic symptoms (Bansal et al., 2018). It has
been discussed that impaired corollary discharge might impair the distinction between self-
and externally caused actions in psychosis, drastically influencing the experience of
selfagency or body ownership (Moberget & Ivry, 2019; Poletti et al., 2019).
Impaired corollary discharge as a basis for altered sense of agency and body ownership
in psychosis might offer a potential model for psychotic symptoms such as delusions of
control or auditory verbal hallucinations (Moberget & Ivry, 2019; Poletti et al., 2019; Thakkar
& Rolfs, 2019). While this indicates that model attempts for linking altered multisensory
processing and psychosis might be feasible for sensorimotor processes (see 4.1 A Lack of
Theoretical Models on Multisensory Processes in Psychosis in the General Introduction),
this evidently is specific for the sensorimotor domain and not suitable for multisensory
processes in general. Nonetheless, this dysfunction in perceptual prediction can be described
within the predictive coding account of psychosis (Sterzer et al., 2018). This account might
provide a means to embed altered sensorimotor processing and its potential role for the
development or upkeep of psychotic symptoms into a greater framework, which might be
suitable to consider various dysfunctions of multisensory processing in psychosis (see 5.1
Causal Inference in the General Discussion).
In sum, previous research indicated deficits in sensorimotor spatial processing and
recalibration in psychosis, which might play a role in disorder development (Bartolomeo et

140
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
al., 2020; Ferri et al., 2016; Noel, Cascio, et al., 2017; Rösler et al., 2015). Previous evidence
offered theoretical links between sensorimotor processing deficits and psychotic symptoms
such as passivity delusions and hallucinations (Moberget & Ivry, 2019; Poletti et al., 2019;
Thakkar & Rolfs, 2019). In contrast, our results on both an intact cumulative and immediate
VAE suggest that sensory-sensory spatial recalibration might be unimpaired in psychosis. One
could speculate that spatial recalibration is specifically impaired in processes, which involve
proprioceptive information, i.e. stimuli involving the own body and behaviour, but intact in
non-proprioceptive and purely external stimuli. This might suggest that sensorysensory spatial
recalibration might not be related to the development of psychotic symptoms or their
maintenance. Evidently, further research on crossmodal spatial recalibration in psychosis is
needed to confirm or reject this hypothesis.
4.2.2 Associations between the VE, the cumulative, and the immediate VAE
We observed significant correlations between the VE and both the cumulative and
immediate VAE over both groups. This is partly consistent with previous studies on
associations between spatial MSI and crossmodal spatial recalibration (see also 1.1 Temporal
Multisensory Processing in Chapter III). Both Bruns et al. (2022) and Rohlf et al. (2020)
observed correlations between spatial MSI and immediate recalibration, but not with
cumulative recalibration. Further, Park & Kayser (2019) reported shared neural substrates in
the medial parietal cortex between spatial MSI and immediate recalibration. Thus, our
findings of a significant correlation between the VE and immediate VAE match previous
evidence, suggesting that spatial MSI and immediate spatial recalibration might be related
processes. While previous work suggested that spatial MSI and cumulative spatial
recalibration might be less closely related (Bruns et al., 2022; Rohlf et al., 2020), this does not
indicate that both processes are independent. It has been proposed that an appropriately
integrated multisensory percept might be crucial for the development of recalibration
processes (Rohlf et al., 2020), suggesting at least a partial association between spatial MSI
and cumulative spatial recalibration. Thus, it could be argued that the correlation between the
VE and the cumulative VAE in our data might match the proposition of Rohlf et al. (2020).
Further, we did not observe a correlation between the cumulative and immediate VAE
over both groups, indicating that the cumulative VEA size was not related to the size of the
immediate VAE. This is consistent with the findings of Bruns & Röder (2015), who also
reported no correlation between cumulative and immediate spatial recalibration. Thus, our

141
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
findings corroborate the proposition of Bruns & Röder (2015) that the cumulative VAE and
the immediate VAE might reflect partially different underlying perceptual processes.
4.2.3 Accumulation of the Immediate VAE
We further explored whether groups differed in the accumulation of the immediate
VAE as a function of consecutive trials with one sound frequency (and direction of AV spatial
disparity), which could give hints if the recalibration rate for immediate recalibration might be
different between patients with the diagnosis of a psychotic disorder and healthy controls.
For the accumulation of the immediate VAE as a function of consecutive trials with
the same frequency, the immediate VAE descriptively increased in patients but remained
stable in healthy controls. However, we did not observe a significant interaction between the
factors group and consecutive trial number of the same frequency. Further, post-hoc tests over
both groups indicated that the immediate VAE did not change as a function of consecutive
same frequency adaptation trials.
For the accumulation of the immediate VAE as a function of consecutive trials with
the different frequency, the immediate VAE decreased with increasing trial number in both
groups. Further, the immediate VAE descriptively reached a minimum value in healthy
controls after two to three consecutive trials and remained stable, while it further decreased in
patients. However, we did not observe an interaction between group and consecutive trial
number. Post-hoc tests over both groups confirmed that the immediate VAE decreased with
increasing different frequency trials. Thus, it can be assumed that the immediate VAE size
reduction as a function of consecutive different frequency adaptation trials was similar in
patients and healthy controls.
Overall, our findings on accumulation of spatial recalibration as a function of the
recent stimulus history are consistent with the findings of the study by Bruns & Röder (2015),
from which we adopted the paradigm. Analogue to our findings, Bruns & Röder (2015)
observed that spatial recalibration decreased with consecutive different frequency adaptation
trials but was not modulated by the number of consecutive same frequency adaptation trials.
Thus, our findings corroborate the authors’ proposition that immediate recalibration might be
primarily impacted by a mismatch between the current spatial conflict and the orientation of
crossmodal spatial disparities in the recent stimulus history rather than a match thereof (Bruns
& Röder, 2015).

142
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
In sum, our patients and controls did not differ in the accumulation of crossmodal
spatial recalibration depending on the recent stimulus history. This suggests that the AV spatial
recalibration rate over short time periods might be similar in patients with the diagnosis and
healthy controls. Interestingly, this is in contrast to evidence on a reduced adaptation learning
rate in visuomotor learning in psychosis (Lencer et al., 2017), further supporting the notion of
intact spatial in contrast to impaired sensorimotor multisensory processing in psychosis.
4.2.4 Sound Localization Biases in Psychosis
Our exploratory analysis of the non-merged data (see 2.4 Data Analysis for a
description of the data merging procedure) largely mirrored the findings of the merged data,
indicating a comparable VE, cumulative and immediate VAE in both groups. However, both
in UA and in AV trials, a non-significant trend for localization bias differences indicated that
patients showed a trend to slightly localize sound stimuli more to the right than healthy
controls, independent of sound frequency and adaptation.
Only few studies investigated sound localization in psychosis. Nevertheless,
localization impairments have been reported, with patients with the diagnosis of a psychotic
disorder showing reduced sound localization accuracy especially in the right hemifield (Perrin
et al., 2010; Sardari et al., 2022). Thus, the non-significant trend for a slightly larger
rightward-bias in our patient sample matches previous findings. However, Sardari et al. (2022)
reported that patients with the diagnosis of a psychotic disorder showed a larger leftward-bias
than healthy controls, thus reporting a bias in the opposite direction compared to our findings.
Our VE/VAE paradigm does not represent a pure sound localization task, since sound stimuli
are either jointly presented with a visual stimulus or influenced by a visual stimulus in the
recent stimulus history. Thus, the comparability of our findings to pure unimodal sound
localization studies (Perrin et al., 2010; Sardari et al., 2022) might be limited. While our
findings are consistent with previous studies and suggest that psychosis might be associated
with sound localization biases, further studies are needed to investigate the extent, variability,
and direction of localization biases in patients with the diagnosis of a psychotic disorder.
Despite only reflecting a non-significant trend, we cannot rule out that a potential
rightward-bias in sound localization influenced spatial MSI and AV spatial recalibration in our
patient sample. However, the descriptive difference over all trials between patients and
controls was rather small, i.e. approximately 1.5 degrees of visual angle. Crucially, our patient

143
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
sample showed comparable localization as indicated by our pre-analysis check for localization
responses relative to speaker location (see 3.1.1 Localization Responses Relative to Speaker
Positions). Thus, it could be argued that a possible influence of this potential, small
rightward-bias on AV spatial processing in our study might be relatively negligible.
4.3 Hypothesis 3: Associations between Spatial MSI, Spatial Recalibration and
Psychotic Symptoms
Our final study aim was to examine associations between spatial MSI as well as
crossmodal spatial recalibration and self-reported psychotic symptoms. In light of the scarcity
of studies on spatial MSI and the lack of studies on sensory-sensory spatial recalibration in
psychosis, no clear expectations regarding associations or direction of possible correlations
between spatial MSI, crossmodal spatial recalibration and psychotic symptoms could be
drawn from the literature. We therefore explored potential correlations between our behavioral
and questionnaire data.
We did not observe any significant correlation between the size of the VE, the
cumulative VAE, or the immediate VAE and self-reports on anomalous perceptual
experiences, hallucinations, paranoia, passivity experiences and negative schemata. Thus, our
findings indicate that spatial MSI and crossmodal spatial recalibration might not be associated
to psychotic symptoms and negative schemata about the self and others.
Previous studies on spatial MSI in psychosis only rarely conducted correlational
analyses between measures of spatial MSI and psychotic symptoms. Nevertheless, our
findings are consistent with a study by Stone et al. (2011) reporting no correlations between
AV far-near judgement performance and negative or positive symptoms. This is further
supported by a study by Stephen et al. (2013), who did not observe associations between
neurophysiological as well as structural measures during an AV far-near judgement paradigm
and positive or negative symptoms. Other studies on spatial MSI in psychosis did not report
correlation data between measures for MSI or neurophysiological measurements during
spatial MSI and psychotic symptoms (de Gelder et al., 2003; Noel et al., 2020; Stone et al.,
2014). Taken together, our findings are in line with findings of Stephen et al. (2013) and Stone
et al. (2011) and offer initial evidence suggesting that spatial MSI and psychotic symptoms
might not be linked to each other.

144
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
In contrast to our findings and previous studies on spatial MSI in psychosis, AV target
detection studies reported correlations between AV stimulus detection and negative but not
positive symptoms (Williams et al., 2010; Wynn et al., 2014), suggesting a potential link
between multisensory processing and negative symptoms of psychotic disorders. It is possible
that we failed to observe correlations between our behavioral and questionnaire data, since we
exclusively focused on positive rather than negative symptoms. Future studies on spatial
multisensory processing in psychosis using a VE/VAE paradigm should investigate if any
association between spatial ventriloquism as well as its aftereffects and negative symptoms
can be observed. However, the lack of correlations between AV far-near judgements and
negative symptoms in the studies by Stephen et al. (2013) and Stone et al. (2011) rather
suggested that there might be no direct association between spatial multisensory processing
and negative symptoms of psychosis.
It is possible that recruiting a larger sample size compared to our study might have
been fruitful in observing statistical significant correlations between the VE, cumulative VAE,
immediate VAE and psychotic symptoms. However, our sample size was either comparable
(Stephen et al., 2013) or larger (Stone et al., 2011) than previous studies reporting no
association between spatial MSI and psychotic symptoms. Further, since no Spearman rank
correlation coefficient ρ approached a potentially meaningful effect size ρ > .3 (see 2.4 Data
Analysis), we argue that larger samples might not significantly change our observed
correlation pattern. Thus, we conclude that our findings suggest that spatial multisensory
processing, i.e. both spatial integration and crossmodal spatial recalibration, might not be
linked to psychotic symptoms. Crucially, this conclusion should be drawn cautiously, since
evidence on associations between spatial MSI and psychotic symptoms is very scarce and
since we are the first to report correlation data between psychotic symptoms and crossmodal
spatial recalibration.
4.4 Limitations
In addition to potential study limitations mentioned above, i.e. a potential overall
rightward-bias in sound localization in the patient group and not having investigated potential
associations between AV spatial processing and negative symptoms of psychosis, the
following possible limitations of our study should be addressed.

145
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Our patient and controls groups differed significantly in age, with patients having a
higher mean age compared to controls. This age difference likely impacted performance in the
TMT and CPT-IP, since performance in both tests has been found to decrease with age,
indicating a decline in processing speed and vigilance over the lifespan (Mani et al., 2005;
Rodewald et al., 2012; Tombaugh, 2004). However, it is unlikely that the age difference
influenced behavioral performance in our experimental paradigm, since previous evidence
suggested that multisensory processing might be rather stable over the adult lifespan and
largely sustained in older adults (Jones & Noppeney, 2021). Further, since we did not observe
group differences in spatial MSI and crossmodal recalibration, we argue that the age
difference might have had limited statistical impact on our behavioral findings.
We observed significant group differences in processing speed and vigilance, reflected
by performance in the TMT and CPT-IP. This indicated that our patient sample had an overall
lower processing speed and vigilance compared to healthy controls, which is consistent with
reports on reduced processing speed and vigilance in psychosis (Gebreegziabhere et al., 2022;
Mesholam-Gately et al., 2009). Crucially, vigilance did however not decrease faster in patients
than controls. This raises the question if lower processing speed and vigilance influenced the
behavioral performance of our patient sample in our VE/VAE paradigm.
However, we did not observe any association between performance in the TMT as well as the
CPT-IP and the VE, cumulative VAE or immediate VAE, suggesting that the performance in
our paradigm was not influenced by group differences in processing speed and vigilance as
measured by the TMT and CPT-IP.
Due to reasons of restricting experimental session duration, we did not include unimodal
auditory or visual localization pretest blocks. Thus, we were not able to obtain estimates of
individual localization performance of sound or flash stimuli independent of crossmodal
stimulus presentation. It could have been possible that differences in unisensory spatial
processing in patients compared to controls, which have previously been reported in psychosis
(Hardoy et al., 2004; Perrin et al., 2010; Sardari et al., 2022), impacted spatial multisensory
processing and sound localization performance in our VE/VAE paradigm. Further, if
unisensory localization differences had been revealed, this would have complicated the
interpretation of possible group effects on spatial MSI or crossmodal spatial recalibration.
However, we did not observe any group difference in spatial MSI and crossmodal
recalibration. Further, our pre-analysis localization performance review procedure (see 3.1.1

146
CHAPTER IV: SPATIAL MULTISENSORY INTEGRATION & CROSSMODAL
SPATIAL RECALIBRATION IN PSYCHOSIS
Localization Responses Relative to Speaker Positions) and the exploratory analysis on the
non-merged data provide estimates of comparable sound localization between our patient and
control samples. Thus, we argue that our behavioral data might not have been influenced by
potential unisensory localization differences between our groups.
4.5 Conclusion
To conclude, our study on spatial MSI and crossmodal spatial recalibration in psychosis
indicates that our sample of patients with the diagnosis of a psychotic disorder showed both
intact spatial ventriloquism and cumulative as well as immediate spatial recalibration.
Although we cannot rule out sampling effects, i.e. having recruited a potentially
highfunctioning outpatient sample (for a comparable argument in our temporal multisensory
processing study, see 4.3.1 Associations between the TBW and Psychotic Symptoms in
Chapter III), we argue that spatial multisensory processing in simple AV stimuli might be
unimpaired in psychosis, since previous studies on spatial MSI already observed intact spatial
MSI as well (de Gelder et al., 2003; Noel et al., 2020; Stephen et al., 2013; Stone et al., 2011,
2014). Thus, we successfully replicated previous work on spatial MSI in psychosis and
extended these findings to AV spatial recalibration. Crucially, our study is the first to report
intact cumulative and immediate AV spatial recalibration in psychosis. Therefore, more
studies are needed to investigate if our findings can be replicated, if they are generalizable to
other stimulus combinations such as visuo-tactile or audio-tactile recalibration and thus to
contribute to the overarching research question of globality vs. domain-specificity of deficient
multisensory processes in psychosis.

Chapter V: General Discussion

In this dissertation project, we investigated multisensory processes in psychosis. The
aim of the project was to study which exact processes of MSI and crossmodal recalibration are
impaired in psychosis. This research aim was based on the initial question if dysfunctions in
multisensory processes are at the root of the marked alterations in perception, which have
been previously reported in psychosis (Javitt & Freedman, 2015; Uhlhaas & Mishara, 2006).
To investigate multisensory processes in psychosis, we conducted three different experimental
studies and compared subjects with and without psychotic symptoms. In order to examine
various domains of MSI in psychosis, we investigated emotional (study 1), temporal (study
2), and spatial (study 3) MSI. Further, we examined crossmodal temporal (study 2) and spatial
(study 3) recalibration in psychosis to provide first evidence for crossmodal learning
processes in psychosis.
In our first study, we aimed to investigated if findings on altered emotional MSI
previously shown in patients with the diagnosis of a psychotic disorder (Lin et al., 2020;
Tseng et al., 2015) could already be observed in psychosis proneness. We administered a
paradigm on emotional MSI using emotional face expressions and vocal prosody (adopted
from Föcker et al., 2011) in healthy subjects with high vs. low psychosis proneness. Contrary
to our expectation, high and low proneness subjects showed comparable performance in
categorizing the perceived emotion of facial expressions and vocal prosody. This could be
observed in unimodal, bimodal emotionally congruent, and bimodal emotionally incongruent
stimulus conditions. This indicates that our sample with high psychosis proneness showed
typical emotional MSI.
In our second study, we aimed to replicate previous findings on impaired temporal
MSI in patients with the diagnosis of a psychotic disorder (Zhou et al., 2018). Further, we
investigated if impairments in temporal multisensory processes in psychosis extend to
crossmodal temporal recalibration. Patients with the diagnosis of a psychotic disorder and
healthy controls completed a SJ paradigm with simple AV stimuli and interleaved adaptation
phases to induce crossmodal recalibration (adapted from Van der Burg et al., 2015). Contrary
to our expectation, patients showed a comparable TBW compared to controls. This indicates
unimpaired temporal MSI in our patient sample, which contrasts previous evidence. Further,
patients and healthy controls showed similar cumulative and immediate temporal recalibration
effects. Thus, our findings indicate intact crossmodal temporal recalibration in our patient
sample.

In our third study, we aimed to replicate previous findings on an intact spatial VE in
psychosis (de Gelder et al., 2003). Further, we examined if previous findings on deficient
crossmodal spatial recalibration observed in the sensorimotor domain (e.g. Bartolomeo et al.,
2020; Rösler et al., 2015) can also be found in sensory-sensory, i.e. AV stimuli. Patients with
the diagnosis of a psychotic disorder and healthy controls completed a paradigm on the VE
and VEA with simple AV stimuli (adapted from Bruns & Röder, 2015). Patients and healthy
controls showed a similar size of the VE. This indicates intact spatial MSI in our patient
sample, replicating the findings of de Gelder et al. (2003). Further, both groups also showed a
comparable size of the cumulative and immediate VAE. This indicates intact crossmodal
spatial recalibration in our patient sample, providing first findings on typical AV spatial
recalibration processes in psychosis.
1 Are Multisensory Integration Deficits in Psychosis Global or Domain-Specific?
While deficits in MSI have been observed in various domains in psychosis, it is still
not sufficiently clear how widespread these deficits might be. Dysfunctional MSI has been
observed in patients with the diagnosis of a psychotic disorder especially in linguistic (Tseng
et al., 2015), temporal (Zhou et al., 2018), sensorimotor (Noel, Cascio, et al., 2017) processes.
Further, it has been reported that emotional MSI might also be impaired, although previous
evidence so far has been inconsistent (Lin et al., 2020; Tseng et al., 2015). In contrast, a
handful previous studies suggested intact spatial MSI (Noel et al., 2020; Stone et al., 2014;
Tseng et al., 2015) and findings of basic multisensory processes such as crossmodal target
detection were inconsistent (Moran et al., 2021; Williams et al., 2010; Wynn et al., 2014).
Overall, the results of our studies do neither offer support for the assumption that MSI
in psychosis might be globally impaired nor that it might be selectively impaired in specific
domains. In all three of our studies, measures of MSI were comparable between subjects with
and without psychosis proneness or the diagnosis of a psychotic disorder, respectively. Our
results thus indicate typical emotional MSI in psychosis proneness and intact temporal and
spatial MSI in patients with the diagnosis of a psychotic disorder. Crucially, while our
findings on emotional and temporal MSI are in contrast to previous evidence in patient
samples and might be due to methodological differences, the findings of our third study
corroborate prior results suggesting intact spatial MSI in psychosis (Noel et al., 2020; Stone et
al., 2014; Tseng et al., 2015).

Thus, embedding our findings into the literature on MSI in psychosis, the existing
evidence overall rather tends to suggest that MSI might be selectively impaired in psychosis
and does not reflect a global dysfunction. This however raises the question why some
domains of MSI are impaired, why others might remain largely intact, and which factors
might influence this selectivity of impairments.
In their review, Tseng et al. (2015) discussed that previous evidence might indicate
that MSI is especially impaired in speech and emotional stimuli, suggesting pronounced
dysfunctions in processing socially relevant crossmodal information. Crucially, social
cognition in terms of unisensory processing difficulties have been reported in psychosis
(Healey et al., 2016; Savla et al., 2013) and it has been discussed that these difficulties might
play a role in the pathogenesis of psychosis (e.g. D. Martin et al., 2020; Seo et al., 2020;
Tripoli et al., 2022). Interestingly, impairments in both unisensory and multisensory
processing was also observed in temporal and proprioceptive/sensorimotor processes, i.e. in
the other domains in which deficient MSI has repeatedly been reported (Noel, Cascio, et al.,
2017; Zhou et al., 2018).
These findings can be reconciled with the notion that MSI deficits might primarily
manifest in domains, which already show marked impairments beyond crossmodal conditions:
in unisensory processes such as facial and vocal emotion processing (Barkl et al., 2014; Gong
et al., 2021; Kohler et al., 2010) or unisensory temporal processing (Amadeo et al., 2022) and
in proprioceptive processes (Borda & Sass, 2015). Inversely speaking, this could indicate that
domains, in which unisensory processes are not or only little impaired, might still largely
benefit from the advantages of MSI, in the sense of intact crossmodal gain ameliorating
potential unisensory performance deficits.
Further, it is also possible that crossmodal gain remains largely intact in psychosis in
less complex tasks, such as spatial processing or target detection with simple stimuli. Initial
evidence for this might be found in studies on AV far-near judgements, which observed
impaired unisensory but similar multisensory performance in patients compared to controls
(Stephen et al., 2013; Stone et al., 2011, 2014). This is further supported by a recent
visuotactile target detection study by Moran et al. (2021) in patients with the diagnosis of a
psychotic disorder. In this study, worse target detection performance was observed in
unimodal conditions in comparison to healthy controls, but performance was similar in
crossmodal trials. Interestingly, earlier ERPs over occipital and frontal regions, which were

discussed to reflect neural substrates of MSI, did not differ between patients and controls.
Moran et al. (2021) concluded that compensatory mechanisms of multisensory processes both
on the behavioural and neural level, due to e.g. the higher attentional capture of crossmodal
stimuli (e.g. Talsma et al., 2009), resulted in comparable target detection performance in
crossmodal trials in both groups (Moran et al., 2021).
In sum, it is possible that in domains with less gravely impaired unisensory
performance or lower task complexity, such as spatial processing or target detection tasks with
simple stimuli, benefits of multisensory processing are still largely preserved in psychosis. In
contrast, MSI might no longer maintain performance benefits in psychosis in domains with
marked unisensory processing deficits and higher task demands, possibly even potentiating
sensory processing impairments. This encourages a more nuanced perspective of earlier
assumptions that unisensory processing deficits in psychosis might result in pronounced
multisensory deficits, based on the non-linear gain nature of MSI (Meredith & Stein, 1996). It
might be possible that this assumption specifically refers to above mentioned domains, which
show pronounced deficits in psychosis, i.e. linguistic, emotional (Healey et al., 2016; Savla et
al., 2013), temporal (Amadeo et al., 2022) and proprioceptive information (Borda & Sass,
2015), but not as much in others such as spatial processing.
We conclude that more research is needed to sufficiently address the question of
domain specific impairments of MSI in psychosis. Specifically, more studies with robust
sample sizes might be needed in domains, which so far have received less scientific attention
than others, such as spatial processing. Moreover, by comparing the level of impairments in
both uni- and multisensory processing in psychosis per domain as well as across domains,
future studies should investigate if MSI might show pronounced deficits in overall markedly
impaired domains, potentially even aggravating unisensory processing dysfunctions.
2 Is Crossmodal Learning Deficient in Psychosis?
While considerable work has been done on MSI in psychosis, no published study
investigated crossmodal, i.e. sensory-sensory recalibration in psychosis. It is thus unclear if
psychosis is associated with dysfunctional adjustment to changes in crossmodal features in
addition to aberrant integration of crossmodal signals. A failure to recalibrate to changes in
crossmodal characteristics might drastically impede the creation and maintenance of holistic
and stable percepts and could thereby contribute to erroneous and fragmented perception,

which has repeatedly been reported in patients with the diagnosis of a psychotic disorder
(Javitt & Freedman, 2015; Uhlhaas & Mishara, 2006).
The results of our two studies on temporal and spatial recalibration, however, do not
offer support for this hypothesis. In our study on crossmodal temporal recalibration, patients
with the diagnosis of a psychotic disorder and healthy controls adjusted their SJ responses in a
similar degree both to prolonged exposure to a fixed AV asynchrony and to the modality order
on the previous AV trial. In our crossmodal spatial recalibration study, patients and controls
showed a similar crossmodal capture effect of sound localization both by prolonged exposure
to a consistent AV disparity and by the direction of crossmodal disparity on the preceding AV
trial. Thus, our results indicate intact cumulative and immediate recalibration both in the
temporal and spatial domain in psychosis. In sum, the findings of our studies on crossmodal
recalibration provide first evidence that sensory-sensory recalibration might be unaffected in
psychosis – in contrast to MSI.
This contrasts previous findings on crossmodal recalibration in the sensorimotor
domain, where it has been observed that patients with the diagnosis of a psychotic disorder
showed impairments in e.g. visuomotor recalibration in prism adaptation and saccadic
adaptation paradigms (Bartolomeo et al., 2020; Lencer et al., 2017; Rösler et al., 2015).
Impairments in sensorimotor recalibration in psychosis have been linked to deficits in
corollary discharge, i.e. a failure to predict the sensory consequences of one’s own behaviour
(Bansal et al., 2018; Thakkar & Rolfs, 2019). It has been suggested that this might constitute a
key factor for the pathogenesis psychosis, which might explain central symptoms of psychosis
such as hallucinations or delusions of control (Moberget & Ivry, 2019; Poletti et al., 2019;
Thakkar & Rolfs, 2019). Thus, dysfunctional corollary discharge mechanisms might offer a
potential model for linking impaired sensorimotor processing and the development of
psychotic symptoms, an issue which has not yet been sufficiently addressed in other domains
of multisensory processing in psychosis.
Crucially, proprioceptive processes have repeatedly been observed to be markedly
impaired in psychosis (Borda & Sass, 2015). This encourages the speculation that crossmodal
recalibration in psychosis might express in a similar pattern of domain specific impairments as
could be assumed in MSI (see 1 Are Multisensory Integration Deficits in Psychosis Global
or Domain-Specific?). Preliminary support for this speculation could be provided by our
third study. It is possible that we did not observe impairments in sensory-sensory spatial

recalibration, because this study focused on an intact domain, namely multisensory spatial
processing. In our second study, however, we did not observe impaired crossmodal temporal
recalibration in psychosis, i.e. in a sensory processing domain in which impairments have
repeatedly been observed in psychosis (Amadeo et al., 2022; Zhou et al., 2018). Thus, the
findings of our second study do not offer support for the speculation of domain-specific
recalibration deficits in psychosis. However, our patient sample in this study showed
unimpaired temporal MSI, contrasting previous evidence (Zhou et al., 2018). This could
indicate that our patient sample had overall rather spared temporal processing capabilities.
Thus, it is possible that our findings on crossmodal temporal recalibration in psychosis might
not be generalizable to the population of patients with the diagnosis of a psychotic disorder.
In sum, our studies provided first results on sensory-sensory recalibration in psychosis,
suggesting intact spatial and temporal recalibration in patients with the diagnosis of a
psychotic disorder. The results of our study on crossmodal spatial recalibration mirror both
our findings and previous evidence on typical spatial MSI in psychosis (Noel et al., 2020;
Stone et al., 2014; Tseng et al., 2015), suggesting that spatial multisensory processing might
overall be unaffected in psychosis. In contrast, the picture is less clear in the temporal domain.
We observed both unaffected crossmodal temporal recalibration and temporal MSI in our
patient sample. The latter, however, contradicts previous evidence on impaired temporal MSI
in psychosis (Zhou et al., 2018). Thus, future studies aiming to replicate our findings are
needed to investigate if the temporal domain might be impaired in psychosis in the integration
but not in recalibration of crossmodal stimuli. Alternatively, a coupling of impaired temporal
MSI and impaired crossmodal temporal recalibration would suggest that temporal
multisensory processing might overall be impaired in psychosis. Given that temporal
processing might be distinctly dysfunctional in psychosis (Amadeo et al., 2022; Ueda et al.,
2018), it could be argued that the latter seems more plausible.
It has been discussed that crossmodal recalibration processes reflect perceptual
adjustment processes in response to changes in crossmodal features such as changed spatial
and temporal relationships. Thus, crossmodal recalibration might play a vital role in the
maintenance of stable and holistic representations of the world (Chen & Vroomen, 2013). This
encourages the question if potential impairments in these processes might be associated with
altered and fragmented perception as it has been previously observed in psychosis (Javitt &
Freedman, 2015; Uhlhaas & Mishara, 2006). To our knowledge, we are the first to provide

experimental evidence on intact sensory-sensory recalibration in psychosis, adding to the
findings of a recent study in rare EOS (Zhou, Cui, et al., 2022). Thus, we encourage further
studies with larger sample sizes and experimental designs covering the whole range of
(multi)sensory processing domains, thus aiming to replicate our initial findings on crossmodal
recalibration in psychosis and to extend them to other domains. Such approaches will
contribute to answering the questions a) if psychosis is associated with intact or impaired
crossmodal recalibration, b) if crossmodal recalibration might be impaired in some domains
but intact in others, c) if crossmodal recalibration in psychosis might show a similar pattern of
domain specific impairments as could be assumed in MSI and d) if potential deficits in
crossmodal recalibration might be associated with the development of psychotic symptoms.
3 Are Deficits in Multisensory Processing in Psychosis a Precedent or a Consequence
of Disorder Development?
In several published studies, it has been discussed that deficits in multisensory
processes might play a role in the development of psychotic symptoms (e.g. Amadeo et al.,
2022; Postmes et al., 2014; Tseng et al., 2015; Wallace & Stevenson, 2014). Impaired MSI
might facilitate the learning of erroneous associations or hinder the appropriate binding of
information (Odegaard & Shams, 2017), which in turn might impede the construction and
maintenance of holistic representations of the environment (de Jong et al., 2009; Postmes et
al., 2014; Uhlhaas & Mishara, 2006). However, so far the majority of studies on MSI in
psychosis have been conducted in patients with the diagnosis of a psychotic disorder using
cross-sectional designs. In order to evaluate if impaired multisensory processes precede the
manifestation of psychosis, studies in samples prior to disorder onset such as healthy subjects
with high psychosis proneness are needed.
The literature so far fails to answer this question due to a relative scarcity of published
studies in psychosis proneness, which focused only on a few domains of multisensory
processing. Thus, previous studies in psychosis proneness did not sufficiently cover all
domains of MSI, preventing generalized conclusions on deficient MSI as a potential key
factor in the development of psychotic symptoms.
Most studies on MSI in psychosis proneness have been conducted in the temporal and
in the sensorimotor domain. In several studies, a positive relationship between the size of the
crossmodal TBW and higher levels of psychosis proneness could be observed (Dalal et al.,
2021; Di Cosmo et al., 2021; Ferri et al., 2017, 2018; Marsicano et al., 2022). These findings

are consistent with previous reports of an enlarged TBW in patients with the diagnosis of a
psychotic disorder (Zhou et al., 2018). In the sensorimotor domain, previous evidence
suggested a weakened sense of ownership over the own body and a higher occurrence to body
representation distortions. This has been indicated by a positive relationship between a
heightened susceptibility to the rubber hand illusion and increased psychosis proneness
(Germine et al., 2013; Kállai et al., 2015; Torregrossa & Park, 2022). Taken together, both in
the temporal and sensorimotor domain, findings in psychosis proneness indicated that MSI
might already be impaired before full-blown psychosis manifests, suggesting that
dysfunctional multisensory processes might play a role in disorder development.
Only few studies investigated linguistic MSI in psychosis proneness. On the one hand,
Muller et al. (2021) observed a higher occurrence of McGurk illusions in subjects with higher
psychosis proneness, suggesting higher susceptibility to the illusion and thus enhanced
linguistic MSI in their psychosis proneness sample. This finding contrasted the authors’
hypothesis and was inconsistent with previous findings in patient samples (Tseng et al.,
2015). On the other hand, Muller et al. (2020) did not observe any association between the
McGurk effect and higher levels of psychosis proneness in healthy subjects, suggesting
typical linguistic MSI in psychosis proneness. Thus, initial findings on linguistic in psychosis
proneness so far are inconclusive, hampering inferences if linguistic MSI might already be
dysfunctional prior to psychosis onset.
Apart from MSI studies in the temporal, sensorimotor, and linguistic domain in
psychosis proneness, to our knowledge no study investigated spatial or emotional
multisensory processing. Particularly, addressing this lack of studies on emotional MSI might
be crucial for understanding how altered processing of social information might contribute to
psychosis. Previous studies discussed a potential role of deficient emotion processing for
psychosis development (D. Martin et al., 2020; Seo et al., 2020; Tripoli et al., 2022; Tseng et
al., 2016) and emotional MSI has been observed to be altered in patients with the diagnosis of
a psychotic disorder (Lin et al., 2020; Tseng et al., 2015). Thus, emotional MSI was
investigated in psychosis proneness in the current dissertation project to address the question
if dysfunctions in emotional MSI might precede the manifestation of psychosis.
Contrary to our hypothesis, we observed comparable emotional MSI between subjects
with high and low psychosis proneness in our study on AV emotion processing. This contrasts
the majority of previous findings in patient samples (Lin et al., 2020; Tseng et al., 2015) and

previous findings on impaired unisensory emotion processing in psychosis proneness (D.
Martin et al., 2020; Seo et al., 2020, S. 202; Tripoli et al., 2022; van Donkersgoed et al.,
2015). While our results do not offer support for the assumption of a role of impaired
emotional MSI for psychosis development, the question thus remains if our findings might be
replicable or rather reflect a finding rather specific for our potentially high-functioning
sample.
In sum, MSI has been rather selectively investigated in psychosis proneness. While
dysfunctions in MSI in psychosis proneness have been observed in temporal (Dalal et al.,
2021; Di Cosmo et al., 2021; Ferri et al., 2017, 2018; Marsicano et al., 2022) as well as
sensorimotor processing (Germine et al., 2013; Kállai et al., 2015; Torregrossa & Park, 2022),
findings in linguistic MSI are inconclusive (Muller et al., 2020, 2021) and no published study
investigated emotional or spatial MSI in psychosis proneness. In our study, we observed
typical emotional MSI in psychosis proneness, which however contrasts findings on
unisensory emotion processing (D. Martin et al., 2020; Seo et al., 2020, S. 202; Tripoli et al.,
2022; van Donkersgoed et al., 2015). Thus, so far the existing evidence does not support clear
conclusions if deficits in MSI generally precede disorder manifestation. However, given
patterns of impaired MSI in the temporal and sensorimotor domain observed both in
psychosis proneness (Dalal et al., 2021; Di Cosmo et al., 2021; Ferri et al., 2017, 2018;
Germine et al., 2013; Kállai et al., 2015; Marsicano et al., 2022; Torregrossa & Park, 2022)
and patient samples (Noel, Cascio, et al., 2017; Zhou et al., 2018), it is likely that analogue
patterns can be found in other domains of multisensory processing. It could be argued that this
might particularly be the case in domains, which have previously been observed to be
dysfunctional in psychosis in uni- and multisensory processes, such as those involving
linguistic and emotional stimuli (Healey et al., 2016; Lin et al., 2020; Savla et al., 2013; Tseng
et al., 2015).
Future studies should look into both linguistic and emotional MSI in psychosis
proneness to evaluate if multisensory processes in these domains might be already
dysfunctional prior to psychosis onset. In light of evidence suggesting unimpaired spatial MSI
in psychosis (Tseng et al., 2015; see also 1 Are Multisensory Integration Deficits in
Psychosis Global or Domain-Specific?), future studies should also investigate if spatial
multisensory processing is intact in psychosis proneness and remains stable over course of
disorder development.

4 Can Anomalous Perceptual Experiences Conceptually Link
Multisensory Processing and Phenomenology of Psychosis?
In this dissertation project, we aimed to explore a potential mechanism linking
experimental findings on multisensory processes and phenomenology of psychosis. This is
important since no convincing link so far has been established, despite published assumptions
on an association between deficient MSI and the development psychotic symptoms (e.g.
Amadeo et al., 2022; Tseng et al., 2015; Wallace & Stevenson, 2014). To our knowledge,
only one tangible model attempt has previously been published. In this account, Postmes et al.
(2014) described how psychotic symptoms might develop as a means to explain an estranged
experience of the self in the surrounding world due to deficient integration of proprioceptive
perceptual processes and internal representations into a holistic percept. However, it is likely
that the mechanism described by Postmes et al. (2014) might rather be specific to
sensorimotor processes and their potential link to delusions of control and passivity
experiences. Thus, it could be argued that the account of Postmes et al. (2014) might not be
feasible to cover both a) the whole range of previous findings on impaired MSI in psychosis
and b) psychosis as a whole syndrome.
As outlined earlier (see 4.2 Anomalous Perceptual Experiences as a Potential Link
between Multisensory Processing and Psychosis in the General Introduction), we argued
that the concept of anomalous perceptual experiences (Bell et al., 2006; Wright et al., 2018)
might be a promising mediator, which could link multisensory processing and psychosis via
the mechanism proposed in the disorder model by Garety et al. (2001). Therefore, associations
between our findings on MSI in subjects with psychotic symptoms, subjects’ responses in the
CAPS (Bell et al., 2006), and psychotic symptoms were investigated in the current project.
In all three of our studies on multisensory processes in subjects with psychotic
symptoms, no association could be observed between experimental measures of MSI and
crossmodal recalibration to anomalous perceptual experiences. Specifically, no significant
correlation was found between the CAPS and 1) emotional MSI in subjects with high vs. low
psychosis proneness, 2) temporal MSI and crossmodal temporal recalibration, as well as 3)
spatial MSI and crossmodal spatial recalibration in patients with the diagnosis of a psychotic
disorder and healthy controls. In contrast, in all three studies, significant strong correlations
could be observed between the CAPS and questionnaires covering psychotic symptoms.

Thus, while our results corroborate a link between anomalous perceptual experiences
and psychotic symptoms, no such association was found to multisensory processes. This
raises several questions regarding potential reasons for this finding beyond those already
discussed earlier in the respective study, i.e. potential power issues due to sample sizes and
reduced variance in multisensory processing between groups due to similar multisensory
performance in patients and healthy controls.
It is possible that the CAPS is conceptually closer to phenomenology of psychosis, i.e.
closer to the psychological level of observation of psychotic symptoms, than it is to
experimental findings of MSI. As such it might not be feasible to offer a conceptual link
inbetween both levels of observation. This is supported by the strong correlations between the
CAPS and measures for psychotic symptoms in our data, indicating a conceptual proximity
between both.
Moreover, the item composition of the CAPS might be a possible reason for the lack of
correlations. Although the CAPS inquires perceptual anomalies across all senses, i.e. vision,
audition, touch, smell, taste and proprioceptive/vestibular experiences (Bell et al., 2006), the
questions are almost exclusively formulated targeting a single sensory modality each. Future
approaches might benefit from applying an instrument, which targets crossmodal rather than
unimodal perceptual anomalies, in order to reveal associations to experimental findings of
MSI.
To conclude, we did not observe associations between our experimental measures of
MSI and crossmodal recalibration, respectively, and self-reports on anomalous perceptual
experiences as measured by the CAPS (Bell et al., 2006). Thus, our findings do not offer
support for our hypothesis that dysfunctional multisensory processing might facilitate the
experience of conscious perceptual anomalies. This suggests that our proposition on a
potential link between MSI and the development of psychotic symptoms based on the
mechanism described by Garety et al. (2001) might not be sufficiently suitable. Future studies
should explore alternative mechanism, via which deficits in multisensory processes might
contribute to the development of psychotic symptoms, as it was previously assumed (Amadeo
et al., 2022; Tseng et al., 2015; Wallace & Stevenson, 2014). It might be beneficial to examine
mechanisms underlying altered multisensory processing in psychosis and relate them to
components addressing altered perception in disorder models of psychosis. A possible target
for future research to understand the underlying mechanisms of multisensory processing in

psychosis and relate them to etiological processes might be found in altered perceptual
inference mechanisms (see 5.1 Causal Inference), as previously observed in psychosis
(Sterzer et al., 2018).
5 Mechanisms Underlying Multisensory Processes in Psychosis
While a considerable number of published studies investigated multisensory processes
in psychosis, the mechanisms underlying dysfunctional MSI in psychosis are still not
sufficiently understood. As proposed above (see 4 Can Anomalous Perceptual Experiences
Conceptually Link Multisensory Processing and Phenomenology of Psychosis?),
examining the mechanisms underlying multisensory processes in psychosis might be
beneficial for understanding how altered multisensory processing might contribute to
psychosis. In the following, I will briefly discuss two lines of research on potential
mechanisms of altered multisensory processing in psychosis: inference mechanisms governing
multisensory processing and neural substrates of MSI in psychosis.
5.1 Causal Inference
As briefly introduced earlier (see 2.1 Multisensory Integration in the General
Introduction), a central problem for the brain during MSI lies within the decision, if
crossmodal stimuli belong to the same event and therefore should be integrated or not (Shams
& Beierholm, 2010). It has been discussed that this problem is solved by the brain by means
of Bayesian inferencing, a principle called causal inference (Körding et al., 2007; Sato et al.,
2007).
Within this inference framework, the likelihood of crossmodal stimuli being integrated
is influenced by two types of variables. For one, the incoming sensory signals derived from
the each of the crossmodal cues are formalized as their respective sensory likelihood. Both
sensory likelihoods describe estimates of the underlying veridical stimuli, weighed by their
reliability. Second, a binding prior, called prior of common cause or p’ common, describes the
likelihood of each crossmodal combination in the absence of sensory input. This prior entails
the a priori estimate for crossmodal stimuli originating from the same cause as opposed to
separate causes. The brain infers if it is more likely that crossmodal stimuli originated from
the same or separate sources based on both types of variables, i.e. their sensory likelihood and
the prior of common cause. More specifically, the causal inference model computes the
probability of causal structure for the origin of crossmodal cues separately for the assumption

of a common and separate causes. The more probable causal structure dominates multisensory
perception, influencing the degree of crossmodal influence and MSI (Körding et al., 2007;
Sato et al., 2007; Shams & Beierholm, 2010).
Alterations in Bayesian inference processes have repeatedly observed in psychosis
(Heinz et al., 2019; Humpston et al., 2019; Sterzer et al., 2018). It has been discussed that
impairments in weighing prior knowledge and sensory input might underlie altered perception
and cognition in psychosis, potentially forming the basis for the development and
maintenance of psychotic symptoms (for a review, see Sterzer et al., 2018). This predictive
coding account of psychosis (Sterzer et al., 2018), is based on earlier work on neural
information processing, which assumed that the brain processes information based on
hierarchical Bayesian inference. Within this framework, the brain weighs incoming sensory
input and prior knowledge of the world by their respective precision. The resulting prediction
error, i.e. the mismatch between input and prior, is then propagated upwards the hierarchy,
used to update prior knowledge and thus to continuously learn and adjust the inner
representations of the self and the environment (Friston, 2005; Mathys, 2011).
Psychosis has been observed to be associated with marked alterations within this
predictive coding framework, i.e. aberrant precision weighing of both sensory input and prior
knowledge and thus maladaptive signaling of prediction errors (Heinz et al., 2019; Humpston
et al., 2019; Sterzer et al., 2018). Thus, alterations in predictive processing might be able to
describe how impaired sensory processing and altered perception contribute to the
development of psychotic symptoms via maladaptive perceptual learning mechanisms. To
date, it is however not sufficiently clear how the alterations in inference mechanisms manifest
in psychosis. Previous studies observed both deficient or excessive weighing of prior
knowledge, sensory input or prediction errors (e.g. Davies et al., 2018; Limongi et al., 2018;
Powers et al., 2017; Schmack et al., 2013, 2015, 2017; Teufel et al., 2015; Weilnhammer et al.,
2020). It has been discussed that these inconsistencies might be explicable by the hierarchical
structure of the predictive coding framework, describing deficient weighing of prior
knowledge in lower levels but excessive weighing in higher levels of the hierarchy (Sterzer et
al., 2018). While it is conclusively understood how alterations in predictive information
processing in psychosis might shape altered perception, models of altered predictive
processing might be nonetheless helpful to understand associations between altered perception
and psychosis. Moreover, investigating aberrant inference mechanisms in multisensory

perception such as causal inference might benefit the understanding of the potential role of
impaired multisensory processing for psychosis.
While alterations in predictive coding have been repeatedly overserved in psychosis
(Sterzer et al., 2018), only very few studies investigated causal inference in psychosis in order
to elucidate dysfunctional mechanisms underlying multisensory processes in psychosis. To
our knowledge only two published studies investigated if psychosis might be associated to
altered causal inference.
Noel et al. (2018) investigated causal inference during temporal MSI in patients with
the diagnosis of a psychotic disorder, patients with the diagnosis of an ASD, and two
respective healthy control groups. In a SJ paradigm with AV speech stimuli, the authors
observed impaired temporal MSI, i.e. an enlarged TBW, in both patient groups. Further, both
groups showed altered causal inference parameters compared to controls, with both patient
groups, however, showing different alterations. While patients with the diagnosis of an ASD
mainly differed in their prior of ascribing a common cause, i.e. p’ common, patients with the
diagnosis of a psychotic disorder showed (trends for) alterations in both p’ common and
sensory likelihood. This suggested that although ASD and psychosis are associated with an
enlarged TBW, the underlying mechanisms might be different. Specifically, deficient temporal
multisensory processes in psychosis might most likely be rooted in a combination of altered
causal priors and unreliable sensory representations (Noel et al., 2018).
Odegaard & Shams (2017) investigated multisensory spatial and temporal processing in
healthy subjects with varying levels of psychosis proneness. Basing their expectations on
previous work on altered weighing of prior knowledge in psychosis (for a review, see Sterzer
et al., 2018), Odegaard & Shams (2017) investigated if higher levels of psychosis proneness
are associated with a lower binding tendency, i.e. prior of common cause, during spatial and
temporal AV integration. Results indicated that individuals with high psychosis proneness
showed a decreased binding tendency in the spatial task, but not in the temporal task. This
suggested that psychosis proneness might be associated with a reduced ascription of a
common cause across spatial dimensions. In contrast, the null findings in the temporal task
might have reflected an averaging issue, with some of the subjects with the highest proneness
ratings showing a reduced, others an increased binding tendency (Odegaard & Shams, 2017).
In sum, previous work on causal inference in psychosis and psychosis proneness
indicated that alterations in the parameters governing causal inference might underlie deficient

multisensory processing in psychosis (Noel et al., 2018; Odegaard & Shams, 2017). These
alterations in causal inference, reflected by altered priors and sensory representations, are
consistent with dysfunctional inference mechanisms in psychosis described by the predictive
coding account (Sterzer et al., 2018). This suggests a global, underlying dysfunction in
Bayesian inferencing in psychosis at the root of both uni- and multisensory information
processing and higher cognition.
However, the findings of Noel et al. (2018) and Odegaard & Shams (2017) should be
interpreted with caution. In both studies, several of the reported results reflected
nonsignificant trends or did not survive multiple comparison correction. Further, findings are
not entirely consistent. Noel et al. (2018) reporting a tendency for altered priors during
temporal MSI in patients, while Odegaard & Shams (2017) did not observe an association
between an altered binding tendency and psychosis proneness in a multisensory temporal task.
Thus, the literature so far only insufficiently addressed causal inference mechanism during
multisensory processing in psychosis. Several open questions remain to be answered:
If altered causal inference processes might reflect a global underlying impairment in
psychosis, how could this explain the heterogeneous findings on MSI in psychosis? How can
a global underlying deficit in p’ common and sensory likelihood explain reduced integration
in e.g. linguistic tasks, but excessive integration in temporal tasks? Does the processing of
complex compared to simple crossmodal information in psychosis interact with a global
underlying dysfunction in causal inference, leading to pronounced dysfunctions in
multisensory processing of speech or emotional cues? How do the findings of Odegaard &
Shams (2017) of a reduced binding tendency in psychosis proneness during a spatial task fit
both previous evidence (Noel et al., 2020; Stone et al., 2014; Tseng et al., 2015) and our
findings suggesting intact spatial MSI in psychosis?
In sum, casual inference in psychosis is still poorly understood. Future studies should
address open questions to contribute to a better understanding how causal inference
dysfunctions might underlie the heterogeneity of multisensory processes in psychosis. For
example, future studies should compare parameters of causal inference in psychosis in a
variety of crossmodal tasks, such as VE paradigms, SJ judgement tasks, and tasks with speech
and emotional stimuli. Alterations of p’ common and sensory likelihood should be compared
across these processing domains and between patients, subjects with high psychosis
proneness, and healthy controls. This approach will aid in answering if alterations in causal

inference might reflect a global deficit in psychosis, or if they might manifest differently
depending on task complexity and domain. Further, embedding evidence on causal inference
in psychosis in the broader framework of the predictive coding account of psychosis (Sterzer
et al., 2018) might build the base for understanding if altered multisensory processes might
contribute to the development of psychotic symptoms via maladaptive perceptual inference
processes.
5.2 Neural Substrates of Multisensory Processing in Psychosis
In their paper, Odegaard & Shams (2017) highlighted the importance of
neurophysiological and neuroimaging investigations to further understand the mechanism
underlying altered multisensory processes in psychosis. Odegaard & Shams (2017) briefly
discussed a potential reason for differences in causal inference during MSI in psychosis based
on the target domain. The authors argued that white-matter disconnectivity reported in
psychosis (Crossley et al., 2016; Friston et al., 2016) might underlie an altered prior of
common cause. It could be argued that differences in recruitment of cortical areas during
multisensory processing depending on target domain might partially explain why the prior of
common cause potentially varies across tasks. Odegaard & Shams (2017) proposed that the
respective regions underpinning various target domains in multisensory tasks, such as the
superior temporal sulcus in speech (e.g. Nath & Beauchamp, 2012) or the intraparietal sulcus
in a spatial task (e.g. Rohe & Noppeney, 2015), are affected to a different degree by structural
white-matter disconnectivity in psychosis. As such, a deficit in the binding tendency, i.e. prior
of common cause, might manifest differently depending on the underlying neural substrates
(Odegaard & Shams, 2017).
Earlier neurophysiological and neuroimaging studies have revealed overlaps in neural
substrates of multisensory processes and symptoms of psychosis. For example, an earlier
study by Kim et al. (2003) reported that activation in the superior temporal sulcus and the
inferior frontal gyrus was involved in both temporal multisensory processes and the
emergence of hallucinations, suggesting a neural link between MSI and psychosis.
A recent systematic review by Gröhn et al. (2022) aimed to investigate previous
evidence on the neural underpinnings of MSI in patients with the diagnosis of a psychotic
disorder. By reviewing EEG, MEG and fMRI studies during MSI in psychosis, Gröhn et al.
(2022) were able to draw preliminary conclusions about aberrant neural processes at the root

of multisensory processing in psychosis. In EEG and MEG studies, patients with the diagnosis
of a psychotic disorder showed altered or reduced cortical responses to crossmodal stimuli or
inverse neural response patterns when contrasting congruent and incongruent stimuli
compared to healthy controls (e.g. Stekelenburg et al., 2013; Szycik et al., 2013). Reduced
oscillatory activity across several bands was observed in psychosis during processing of
crossmodal stimuli, suggesting crossmodal information processing deficits
(Balz et al., 2016; Roa Romero, Keil, Balz, Gallinat, et al., 2016; Roa Romero, Keil, Balz,
Niedeggen, et al., 2016). These impairments were observed predominantly over parietal,
occipital and fronto-temporal areas (e.g. Balz et al., 2016; Liu et al., 2016; Sanfratello et al.,
2018) and aberrant neural activity was observed especially in regions covering the superior
temporal sulcus, superior temporal gyrus and the inferior temporal gyrus (e.g. Stekelenburg et
al., 2013; Straube et al., 2014; Szycik et al., 2013). However, conflicting findings were also
observed, reporting no group differences in cortical responses to crossmodal stimuli or even
increased neural signaling in patients compared to controls, which suggested intact or
enhanced MSI (Müller et al., 2014; Stone et al., 2011). Further, fMRI studies revealed reduced
functional connectivity predominantly between the superior temporal sulcus and frontal
regions as well as between the inferior frontal gyrus and various cortical areas (Straube et al.,
2014; Szycik et al., 2013).
Overall, the results of the review by Gröhn et al. (2022) suggested reduced or at least
altered neural responses to crossmodal stimuli and functional disconnectivity between
networks involved in processing of crossmodal information. This offers support for the
assumption that altered neural mechanisms such as deficient neural signaling or impaired
cortical connectivity might underlie dysfunctional MSI in psychosis (Gröhn et al., 2022;
Odegaard & Shams, 2017).
However, it is important to note that only studies on AV information processing in
psychosis could be included in the review, revealing a lack of evidence on neural substrates in
other crossmodal stimulus combinations. Further, the result pattern was not entirely
consistent, with some studies reporting no group differences or even enhanced neural
multisensory facilitation effects in psychosis (Müller et al., 2014; Stone et al., 2011). Gröhn et
al. (2022) argued that previous studies differed to a significant extent in task complexity and
experimental design, which might be a possible reason for the observed heterogeneous
findings. Crucially, the response pattern was judged as not sufficiently consistent to

hypothesize about concrete influencing factors (Gröhn et al., 2022). Lastly, alterations in
neural activity in psychosis were repeatedly not mirrored by behavioural multisensory
impairments (Gröhn et al., 2022).
It is possible that altered neural activity during multisensory processing in psychosis
might not necessarily translate into impaired behavioural performance. It would be interesting
to investigate if altered neural responses in ERP, oscillatory activity or functional
disconnectivity could have been observed in our psychosis samples, which did not show
behavioural differences in emotional, temporal, and spatial multisensory processing compared
to control subjects. It is possible that multisensory behavioural performance might be partially
able to compensate for altered neural substrates in psychosis, leading to typical behavioural
MSI compared to healthy controls. Preliminary support for this hypothesis can be found in
two earlier AV far-near judgment studies. Stephen et al. (2013) observed reduced parietal
MEG responses to AV stimuli in patients with the diagnosis of a psychotic disorder. Stone et
al. (2014) showed altered gamma-band oscillations frontal regions as well as in visual and
auditory cortices in response to AV stimulation in psychosis. In both studies, neural findings
were not associated with multisensory behavioural performance (Stephen et al., 2013; Stone et
al., 2014).
It could be argued that the to date published evidence on neural alterations
underpinning multisensory processes in psychosis partly mirrors the evidence on behavioural
findings. In various studies, dysfunctions or at least alterations of multisensory processes
could be observed, but results seemed to be inconsistent and sometimes contradictory (Gröhn
et al., 2022; Tseng et al., 2015). Although Gröhn et al. (2022) observed no apparent difference
in result patterns between social and non-social designs, it might be possible that alterations in
neural substrates of MSI in psychosis might potentially be influenced by similar factors as
behavioural studies such as symptom severity (Lin et al., 2020), stimulus complexity (Darke
et al., 2021; Tseng et al., 2015) or the target domain of multisensory processing (e.g. Tseng et
al., 2015; Zhou et al., 2018).
We conclude that future studies on multisensory processing in psychosis should
include neurophysiological and neuroimaging techniques to elucidate the potential impact of
these proposed factors. Studies in patients with the diagnosis of a psychotic disorder should
combine behavioural measurements and neural markers of multisensory processing to
investigate if behavioural performance might partially compensate for alterations in neural

substrates. Further, studies should investigate neural substrates of MSI in psychosis proneness
to evaluate if neural processes underpinning MSI might be already altered prior to disorder
onset. This would aid in understanding the developmental trajectory of multisensory processes
in psychosis and shed further light on the insufficiently answered question if aberrant MSI
might play a role in the development of psychosis (see 3 Are Deficits in
Multisensory Processing in Psychosis a Precedent or a Consequence of Disorder
Development?).
6 Limitations and Outlook
In this dissertation project, we recruited stable outpatients as patient samples for the
studies on temporal and spatial multisensory processing. It is possible that our patient samples
differed in in-/outpatient status compared to previous studies and as such might be dissimilar
in impairments beyond those tested in our studies, such as functioning level. Further, it could
be argued that the patient samples of previous studies might differ in hitherto unaddressed
factors, which could have an impact on multisensory processing, such as motivation,
concentration or neuro-cognitive capacities. These differences could be due to variations in
in-/outpatient status in previous studies. As such, these factors might partially account for
performance differences observed in previous studies.
Thus, we argue that it might be important to review, which factors might be partial
confounds in explaining the difference in multisensory processes between patients and healthy
controls. For example, inpatient status might be associated with a higher level of general
impairment than outpatient status. By not accounting for such potential group differences, the
specific role of psychosis on group differences in multisensory processing might be
overestimated.
To compare the patient status in previous studies to our patient samples, we reviewed
published studies on temporal and spatial multisensory processes in psychosis. This revealed
that the in-/outpatient status considerably varied between studies, with either outpatient (de
Boer-Schellekens et al., 2014; de Gelder et al., 2003; B. Martin et al., 2013; Wynn et al., 2014;
Zopf et al., 2021), inpatient (Zhou, Lai, et al., 2022; Zvyagintsev et al., 2017) or mixed
samples (Haß et al., 2017) reported. Further, several studies did not sufficiently specify if in-
or outpatient samples were recruited (Foucher et al., 2007; Noel et al., 2018, 2020; Stephen et
al., 2013; Stevenson, Park, et al., 2017; Stone et al., 2011, 2014; Vanes et al., 2016; Williams

et al., 2010). Thus, it might be difficult to assess to what extent in-/outpatient status could
have influenced group differences in multisensory processing in previous studies in
comparison to our findings.
Next, we briefly reviewed reports on symptom severity in previous studies as a potential
estimate, if the level of impairments might have differed between studies. Most of previous
studies on temporal and spatial multisensory processes in psychosis reported scores for the
PANSS positive and negative subscale, an instrument measuring positive and negative
symptoms of psychotic disorders (Kay et al., 1987). Overall, previous studies reported mean
scores of approximately 14-16 points per subscale (Noel et al., 2018, 2020; Tseng et al., 2015;
Zhou et al., 2018; Zhou, Lai, et al., 2022; Zopf et al., 2021), which might correspond to a
status of no acute illness (Leucht et al., 2005). Since previous studies suggested that samples
might not have differed greatly in impairment level, we think it is unlikely that variations in
symptom severity or general impairment account for group effects on multisensory
processing.
Crucially, our short review of the literature for differences in patient status and symptom
level was done post-hoc. Future studies on multisensory processes in psychosis should recruit
two samples of in- and outpatients, respectively, and compare them to healthy controls. These
approaches should investigate concrete factors, which differ between the two patient groups,
such as functioning level, symptom severity, concentration or motivation, and test if these
factors partially account for dysfunctions of multisensory processing. This approach would be
helpful in order to rule out confounding factors, avoid overestimating the specific impact of
psychosis on multisensory processing, and contribute to a clearer understanding of the
association between psychosis and multisensory processes.
It is important to note that we relied on AV processes as an operationalization of
multisensory processes in psychosis. While this mirrors the majority of designs in previous
studies on MSI in psychosis (Lin et al., 2020; Tseng et al., 2015; Zhou et al., 2018), this limits
the generalizability of our findings to other crossmodal stimulus combinations. Some previous
findings suggested that impairments in MSI might be affected by the targeted sensory
modality, for example in the emotional domain (Lin et al., 2020; Tseng et al., 2015). However,
studies beyond the AV stimulus combination in psychosis are rare. This highlights the
importance for future studies to investigate other crossmodal stimulus combinations in order
to obtain a comprehensive picture of multisensory processes in psychosis.

As outlined above, our findings only partially corroborate previous findings on
multisensory processes in psychosis. While we were able to replicate findings on intact spatial
MSI in psychosis, we did not observe expected impairments in emotional MSI in psychosis
proneness and temporal MSI in patients with the diagnosis of a psychotic disorder. While we
contributed first findings suggesting typical emotional MSI in psychosis proneness and intact
crossmodal recalibration in the spatial and temporal domain in psychosis, more studies are
needed in order to confirm these results. Overall, our findings and their discussion with regard
to previous evidence suggest a complex pattern of multisensory processes in psychosis, which
likely does not reflect a single, globally impaired process but rather an interplay of a
multitude of factors influencing if some multisensory processes might be negatively affected
or relatively spared in the disorder.
In our findings, some hints for such possible factors were observable, which should be
addressed in future research. As discussed throughout this dissertation, the most apparent
factor might lie in the target domain of multisensory processes, meaning if spatial, temporal,
emotional, linguistic or sensorimotor processes are involved. Previous evidence suggested
impairments in psychosis especially in domains with more complex information, i.e. mainly
linguistic, temporal, sensorimotor and (albeit inconsistently) emotional stimuli (Lin et al.,
2020; Noel, Cascio, et al., 2017; Tseng et al., 2015; Zhou et al., 2018). However, the
assumption of impaired emotional and temporal MSI was not supported by our findings,
indicating that the notion of domain-specificity might not yet be comprehensively understood.
As we discussed earlier (see 1 Are Multisensory Integration Deficits in Psychosis Global
or Domain-Specific?), it is possible that impairments in multisensory processes might
particularly manifest in domains, which already show pronounced deficits in unisensory
processing. Other potential factors determining how emotional multisensory processing
impairments manifest might be found in the task-relevance of the attended modality (Thaler et
al., 2013), stimulus complexity such as static or dynamic stimuli (Darke et al., 2021), emotion
category or valence (e.g. Bonfils et al., 2020; Tripoli et al., 2022), symptom severity (Lin et
al., 2020) or the respective association with positive vs. negative symptoms of psychotic
disorders (e.g. Williams et al., 2010; Wynn et al., 2014). This suggests that a more finegrained
approach in investigating multisensory processes in psychosis might be needed to elucidate
the potential impact and interaction of above proposed factors.

A crucial line of research for future study will be to elucidate exact mechanisms, by
which altered multisensory processes might contribute to psychosis. In this dissertation
project, we provided first evidence that anomalous perceptual experiences (Bell et al., 2006;
Garety et al., 2001) likely is not the central mechanism, suggesting that other factors might be
more relevant. This calls for more studies on the following three aspects. First, future studies
should examine multisensory processes in psychosis proneness or first degree relatives –
especially in underrepresented domains such as emotional, linguistic and spatial processing.
This will aid in understanding the developmental trajectory of multisensory processes in
psychosis and if impairments thereof might constitute a risk factor for the disorder. Second,
investigating the underlying neural substrates (Gröhn et al., 2022) and causal inference
processes (Noel et al., 2018; Odegaard & Shams, 2017) of multisensory processing in
psychosis will contribute to understand potential dysfunctions in neural and computational
mechanisms at the root of multisensory processes in psychosis. Finally, by integrating
evidence from different observational layers, i.e. behavioral, neural, and computational
findings, future studies should aim to provide models describing the contribution of altered
multisensory processes for psychosis. A potential, promising candidate framework can be
found in computational approaches such as the predictive coding account of psychosis
(Sterzer et al., 2018). However, more research especially on causal inference in psychosis is
needed to understand how dysfunctions in multisensory processes in psychosis might be
explainable in a predictive coding perspective.
7 Concluding Remarks
This dissertation project aimed to contribute experimental evidence on multisensory
processes in psychosis. This research aim was built on the hypothesis that altered integration
and recalibration of crossmodal information is associated with maladaptive learning and thus
contributes to psychosis. The available literature suggested that deficient integration of
crossmodal signals might facilitate fragmented perception (Postmes et al., 2014; Uhlhaas &
Mishara, 2006) and lead to false inferences on the cause of the sensory information (Odegaard
& Shams, 2017). Further, excessive integration might facilitate erroneous binding of
information originating from separate sources and thus lead to confusing percepts and the
maladaptive learning of perceptual associations (Amadeo et al., 2022; Odegaard & Shams,
2017; Zhou et al., 2018).

The findings of this dissertation project do not support the notion that deficits in
multisensory processing in psychosis reflect a global dysfunction. Given the lack of group
differences in all three of our experiments, our findings however also fail to offer support for
the assumption of a domain-specificity of multisensory processing deficits. Our results might
suggest that altered perception in psychosis is not generally driven by dysfunctions in
multisensory processing. While the studies in this project did not confirm impairments in
emotional MSI in psychosis proneness and deficient temporal MSI in patients with the
diagnosis of a psychotic disorder, we observed typical spatial MSI in psychosis, replicating
previous findings (de Gelder et al., 2003; Noel et al., 2020; Tseng et al., 2015). More studies
are however needed to disentangle factors, which could explain why our subjects did not show
dysfunctions in emotional and temporal MSI, as previously reported in psychosis (Lin et al.,
2020; Tseng et al., 2015; Zhou et al., 2018).
Further, to our knowledge the studies in project are the first to provide evidence on
crossmodal spatial and temporal recalibration in patients with the diagnosis of a psychotic
disorder. Our results indicate that psychosis might be associated with intact cumulative and
immediate recalibration processes in both domains. Thus, the findings of this project suggest
that aberrant perception in psychosis might not be associated with dysfunctional perceptual
adjustments to changes in crossmodal characteristics.
The findings of this project did not corroborate that deficits in emotional MSI precede
psychosis onset. This in turn does not offer support for the notion that impaired MSI overall
plays a role in disorder development. Future lines of research should target concrete
mechanisms how altered multisensory processes might contribute to psychosis. In this project,
a proposed mechanism describing that dysfunctional multisensory processes might facilitate
anomalous perceptual experiences (Bell et al., 2006; Garety et al., 2001) was not supported by
our findings.
A road for future research is to relate findings of multisensory processing in psychosis
to neural substrates as well as computational mechanisms of perception to elaborate on
mechanisms underlying multisensory perception in psychosis. Further, approaches to
formulate models how multisensory processing might be linked to psychosis should
incorporate relevant factors and empirically test how these add to the explanatory value of a
disorder model. It is likely that an interplay of factors such as task and stimulus complexity,

involved sensory modalities, alterations in neural substrates and dysfunctions in underlying
computational processes governs how multisensory processing manifests in psychosis.


