


NAVIGATING THE PANDEMIC: COMPARATIVE ANALYSES AND
THEORETICAL INSIGHTS IN POLICY-MAKING AND
IMPLEMENTATION DURING COVID-19
CHAPTER 1 NETWORK GOVERNANCE IN CHINESE LOCAL
GOVERNMENTS
1.1 Chapter Overview
Combining the network governance model with knowledge of emergency management, this
manuscript analyzes the performance of Hubei and Sichuan provincial governments in
response to COVID-19 in early 2020. This study reveals that network governance, as seen in
the Chinese response to COVID-19, does not closely resemble any of the three well-known
forms of network governance in the literature. Instead, although the prevailing governance
structure mimics some elements of the Network Administrative Organization form, it exhibits
some uniquely Chinese characteristics. This manuscript also argues that core leaders’
characteristics, mass media roles, and path-dependent adherence to systems created earlier
significantly affect the resulting network governance. This manuscript also provides
suggestions for improving the effectiveness of network governance of emergency
management in China’s centralized system. These suggestions are specifically designed to
complement the unique characteristics and requirements of China's governance structure,
ensuring a strategic, resilient, and responsive approach to managing emergencies effectively
within the country's distinct administrative framework.

Keywords: COVID-19, network governance, provincial government, Chinese characteristics,
comparative studies
1.2 Research Question and Significance
In early January 2020, COVID-19 became China's major public health emergency. One after
another, provincial governments carried out emergency management policies in response.
Due to varied performances in pre-disaster preparation and response stages, epidemic
prevention and control, and the speed and effect of local economic recovery, they differed
across the provinces. This manuscript raises the following research questions: RQ1a: Did the
Chinese response to COVID-19 adhere to existing network governance forms as depicted in
the literature? RQ1b: If not, how did network governance differ for the Chinese context?
RQ2: How did the response vary between Hubei and Sichuan provinces, and what are the
implications for a Chinese network governance model? Moreover, RQ3: If China's general
political and administrative environment remains unchanged, what strategies can be more
effective for government leaders to fine-tune network governance to accommodate the unique
Chinese context and improve public health emergency management? According to Hofstede
(2001), differences in governmental and societal systems are sometimes described as the
result of different cultures and other times represented as the result of different emergent
institutional systems (North, 1991); I suspect the differences in network governance in China
are primarily because of institutional differences including centralized system and top-down
mechanism of governance.

Based on the characteristics of a strong government’s unique administrative model, this
manuscript explores how two Chinese provinces performed their respective functions,
mobilized public resources, and cooperated with external organizations. Thus, my
comparative cases examine how public and private hospitals, social media, private
enterprises, and tried to universities responded to this public health crisis, safeguarded public
interest, and reduced economic losses. Hubei and Sichuan Provinces provided valuable
information for emergency managers and researchers to look for differences in responding to
the outbreak.
1.3 Literature Review and Background of Response to COVID-19 in Hubei and Sichuan
1.3.1 Literature Review: Form of Network Governance
A network consists of a set of nodes, or actors, and the ties between these nodes (Borgatti et
al., 2013). These nodes can be persons, teams, organizations, regions, countries, and so on
(Borgatti et al., 2013). These ties, which connect actors in networks to each other, can
represent relations among the nodes, such as friendship, knowledge exchange, advice
seeking, competition, collaboration, and so on (Carpenter et al., 2012). Compared with formal
hierarchies and pure-form markets, networks have advantages in promoting learning,
enhancing organizational legitimacy, and producing economic benefits (Podolny & Page,
1998).

As for network governance, some researchers define it as a form of governing where public,
nonprofit, and private sectors are involved in collective action and consensus-oriented
decision-making (Ansell & Gash, 2008; Emerson et al., 2012; Kapucu, 2012). It is also
defined as “the use of institutions and structures of authority and collaboration to allocate
resources and to coordinate and control joint action across the network as a whole” (Bryson et
al., 2006;
Isett & Miranda, 2015; Kapucu, 2012; Provan & Kenis, 2008). Network governance can
advance understanding of “the internal mechanics of collaborative governance instances”
(Kenis, 2016, p. 155). In particular, the network approach to governance addresses how
“specific cases of governance develop, function, and perform” by focusing on “how the
governance, leadership, and management of relationships between the actors involved are
structured” (Kenis, 2016, p. 155).
Milward and Provan (2006) suggested three types of network governance structures:
participant-governed networks or shared governance, which is the simplest and most common
form of network governance and depends exclusively on the involvement and commitment of
its members; lead organization-governed networks, which are highly centralized and brokered
with asymmetrical power; and governance structures led by a Network Administrative
Organization (Hereafter NAO). With the NAO framework, a separate administrative entity is
set up expressly to govern the network and its activities.
Specifically, network effectiveness is how a network achieves its organizational, community,
or network-level goals (Kapucu & Hu, 2020). There are four critical predictors for achieving
effectiveness in the three network governance forms: Trust, number of participants, goal

consensus, and the need for network-level competencies (Provan & Kenis, 2008). Based on
these four key predictors, Provan and Kenis (2008) also pointed out how each network
governance form can most effectively achieve network-level outcomes. The shared network
governance model will be most effective when trust is widely shared within the high-density
network and among its decentralized and relatively few participants. The shared network
governance model also requires high network-level goal consensus but a low need for
networklevel competencies. Lead organization governance models can be effective even
when trust is narrowly shared among a moderate number of participants. The lead
organization model will likely have low network-level goal consensus and a reasonable need
for network-level competencies. The NAO network governance can be effective when trust is
moderately to widely shared among the network’s participants and there is a moderate to
large number of participants. Also, within the NAO model, network-level goal consensus is
usually moderately high, and the need for network-level competencies is high. This
manuscript suggests that from a macro-level perspective, when the number of network
participants keeps increasing and the jurisdiction of the network’s responsibilities expands,
the NAO governance model becomes the most effective form. This configuration permits
network governance operators to satisfy most participants' needs and handle complicated
issues effectively.
As for the NAO form, four critical predictors of the effectiveness of network governance can
be interpreted as follows (Provan & Kenis, 2008). First, trust can be interpreted as one
relationship characteristic that reflects “the willingness to accept vulnerability based on

positive expectations about another’s intentions or behaviors” (McEvily et al., 2003). Within
the NAO form, trust can be lower compared with the shared governance model, for its
members are called upon to collectively monitor the actions of NAO leadership (Provan &
Kenis, 2008). Even so, NAO needs to develop trust and good working relationships with the
member organizations for effective knowledge sharing (Huang, 2014).
Second, as for the number of participants, the NAO form can facilitate many diverse
participants due to its unique administrative structure (Provan & Kenis, 2008). The NAO
form is likely to be most effective in networks with the most significant number of
participants. Because it has its unique administrative structure, it will be able to handle more
significant numbers of diverse participants and the complexity brought by social issues and
increasing numbers of various participants.
Third, the NAO form requires more significant involvement by at least a subset of network
members. These participants are typically committed to network-level goals and are
strategically involved with the network (Provan & Kenis, 2008). NAO leaders and staff must
work with participants daily and cope with potential conflicts, enhancing commitment to the
network and its goals. Thus, goal consensus can be moderately strong in the NAO form.
Lastly, when it comes to the network competencies, with an NAO, although there may be
significant size and resource constraints, it is the job of the network-level staff to develop the
skills needed for network-level action (Provan & Kenis, 2008). The NAO form requires more
significant involvement by at least a subset of network members. These participants are

typically committed to network-level goals and have a strategic involvement with the
network.
1.3.2 Background: Chinese Context
China is a country with the largest population and largest governmental structure in the world.
To operate this considerable vessel effectively, governance in China needs a complex form of
network governance that can effectively respond to the challenges and promote economic and
social development. Within the framework of state-society relations, China adopts a
centralized “state-centered top-down approach” (Sellers, 2011). Some observers describe the
government of China as an authoritarian political system under the political leadership of the
Chinese Communist Party (hereafter: CCP) (Minzner, 2011; Wang, 2015). Following
Minzner (2011) and Wang (2015), Chinese provincial governments are under the jurisdiction
of the central government, and, in turn, they supervise the municipal governments within their
jurisdictions. Because of their robust governance mode, all levels of government are
dominant in public resource mobilization and organizational capacity. Thus, local officials
manage social affairs through top-down policies. This is especially evident in the face of
large-scale disasters, for which governmental leaders claim advantages of “nationwide
systems.”
Freedom House (2020) suggests that in countries with highly centralized governments, social
organizations and people outside the government rarely express ideas and behaviors that go
against the government, and they do not question the government’s claims, even when their

strategies are realistic. Organizational power and centrality depend on the nature and the
context of the participants in network governance (Hoffman et al., 1990; Keast et al., 2004).
Under these conditions, one can see that Chinese governments can quickly mobilize and
concentrate the required public resources to accomplish a series of significant actions. This
may also present a potential problem: the government directly implements the evaluation of
government decision-making. Under these circumstances, lack of supervision, power
rentseeking, and corruption may occur. Thus, one might question fairness and impartiality
towards some network participants.
This manuscript will extend our understanding of Provan and Kenis’ (2008) key factors that
influence the effectiveness of network governance forms by examining the governance forms
implemented by the Chinese government in response to COVID-19. Specifically, the
governance and actions of two Chinese provinces will be studied and compared to each other
and Western countries.
1.3.3 Historical Precedence for Chinese Characteristics Network Governance of Public Health
Emergencies
China experienced the impact of SARS in 2003. To deal with the virus effectively, China
passed the Regulations on Emergency Response to Public Health Emergencies on May 7,
2003, which was officially implemented two days later. After SARS was effectively
controlled, on August
28, 2004, the Law on the Prevention and Control of Infectious Diseases, passed on February
21, 1989, and implemented on September 1 of the same year, was revised again. At the same

time, the Emergency Response Law was passed on August 30, 2007, and implemented on
November 1 of the same year. In 2009, the H1N1 influenza pandemic caused 120,498
confirmed cases and 648 deaths in China (Tang, 2010). Since then, China has revised the
Regulations on Public Health Emergencies on January 8, 2011, and the Law on the
Prevention and Control of Infectious Diseases on June 29, 2013, to improve the response
level to public health emergencies. These suggest that, guided by relevant laws and
regulations, the Chinese government has continuously strengthened the governance of the
epidemic prevention network to improve its management capabilities in early warning,
decision-making, resource allocation, treatment implementation, and post-pandemic recovery.
Article 3 of the Law on the Prevention and Control of Infectious Diseases classifies infectious
diseases into Types I, II, and III. Type I refers to plague and cholera. Type II includes
infectious atypical pneumonia, AIDS, viral hepatitis, avian influenza, etc. Type III has
influenza, mumps, rubella, etc. Article 4 of this law stipulates that among the Type II
infectious diseases, SARS, pulmonary anthrax, and highly pathogenic avian influenza,
prevention and control measures for Type I contagious diseases should be taken. For sudden
infectious diseases of unknown cause, where prevention and control measures for Type I
infectious diseases as referred to in this Law need to be taken, the health administrative
department of the State Council shall promptly report to the State Council for approval and
announce and implement them.
1.3.3.1 Core Government Leaders’ Characteristics

Leaders are expected to be flexible and adaptable to the changes in their environments
(Kapucu & Hu, 2020). However, under a centralized system, the core leaders are compelling
and have dominant roles in public affairs, especially in public health emergencies. March
(1994, p.141) defined power as “the capability to get what you want or to fulfill your
identity.” I suggest that China’s centralized government and provincial magistrates (provincial
party secretary and governor) tend to dominate, which means that independence for external
organizations and individuals is limited, for they need to conform to government orders.
Organizations with more resources in the network might have more power, control, and
authority in decision-making (e.g., Kelman et al., 2013; Klijn & Koppenjan, 2016; Pfeffer &
Salancik, 1978). In this situation, an organization that is more central in the network will have
more power (e.g., Brass & Burkhardt, 1992; Choi & Robertson, 2014; Scott & Davis, 2007).
Following Nohria (1992), the characteristics of Chinese governmental leaders can also be a
significant predictor for the effectiveness of the network. These may include charisma,
expertise, gender, education, formal role or position, control of critical resources and
information, and potential gatekeeping function. Due to the characteristics of strong
government and the lack of external monitoring from citizens, social groups, and other
branches of government, the competencies of individual leaders are more crucial to ensure the
effectiveness of network governance.
1.3.3.2 Mass Media’s Roles and Effects
Media can convey knowledge sharing and information exchange, critical elements of
effective network governance. Knowledge management aims to identify, extract, and capture

knowledge-based assets to utilize them best to achieve goals (Agranoff, 2008). Knowledge
sharing and management provide participants access to others’ information and knowledge
and can help public organizations respond to environmental uncertainty and complexity
(Dawes et al., 2009). These ideas suggest that information exchange is a crucial function for
interorganizational networks. Organizations utilize existing ties or build new connections to
access helpful information or distribute information in networks (Kapucu & Hu, 2020). A
wellconnected network fosters smooth communication processes and allows timely
information exchange (Koliba et al., 2010; Milward & Provan, 2006). Also, effective
exchange of information and knowledge management should be emphasized to obtain
information and respond to emergencies promptly because these are indicators of high-
performing networks (Popp et al., 2014).
In public health emergencies, social media has become significant. Some media provide
platforms for content production and communication based on user relationships on the
Internet. Some media can facilitate interpersonal communication, information sharing, and
cooperation (Fung et al., 2015). For an increasing number of people, social media should be a
ubiquitous tool and support administrative, private, and professional use, such as a source of
information, news, entertainment, or networking (Ventola, 2014; Vraga et al., 2018). In the
field of public health, social media can facilitate informative communication of disease risks
and intervention and dissemination of healthy lifestyles and public health policies. Some
media can also serve as potential data sources for public health testing to complement
traditional disease surveillance and be valuable for tracking epidemics (Li et al., 2020).

China’s mass media comprises institutional, market-oriented, and online media (Tian & Zhu,
2015). Institutional media are organized and led by the CCP, which include central and local
press and official new media, which contribute to the purpose of governance and play a role
in organizing and guiding public opinion (Guo et al., 2005). Market-oriented press emerged
in the 1980s and accelerated in the 1990s (Shirk, 2011), changing from the sole proprietorship
of government agencies to today’s increasing role for private ownership (Xu & Albert, 2017).
In the early 1990s, the Chinese government authorized these media to undertake private
revenueraising (Guo et al., 2005). Online media include business news websites and other
outlets created by private citizens. After obtaining an “Internet News Information Service
License” issued by the Cyberspace Administration of China (CAC), commercial news
websites can engage in specialized news reporting, editing, publishing news reviews, etc., to
attract readers and generate income. Privately created media consists of content creators,
including Weibo, WeChat public accounts, and other forms, and have become minors' primary
source of news information (Ji et al., 2018).
1.3.3.3 Path Dependence
Path dependence (Arthur, 1989) may also relate to how network governance unfolded in
response to COVID-19. Path dependence means that past policies determine the future
development of economic systems or policies. At a broad level, path dependence refers to the
fact that what happens at an early stage affects the outcome of subsequent events (Sewell,
1996). In a narrow sense, path dependence means that once a country or region starts to
embark on a particular “track,” the cost of reversal will be very high. Even if there are other

options, various factors make it challenging to achieve easy reversal (Levi, 1997). A distinct
yet closely related concept to path dependence is the concept of imprinting, which captures
how initial environmental conditions leave a persistent mark (or imprint) on organizations
and organizational collectives (such as industries and communities), thus continuing to shape
organizational behaviors and outcomes in the long run, even as external environmental
conditions change (Marquis, 2013).
1.4 Methods
This study conducts a comparative case analysis (Hamel, 1993; Merriam, 1988; Stake, 1995;
Yin, 2018) between Hubei and Sichuan Provinces in their COVID-19 responses. I sought data
for significant indicators, such as the number of COVID-19 cases, as a valuable measure of
policy effectiveness. This study uses multiple data sources, including media reports,
government archives, and datasets summarized by the Health Commissions of these two
provinces. This study compares the performances of these provinces during pre-disaster
preparation, response, and post-disaster recovery phases. These three phases derive from the
U.S. Integrated Emergency Management System (IEMS) created by FEMA leaders (Federal
et al., 2010; Giuffrida, 1985). I identify the foremost provincial leaders, specialized
bureaucrats, social organizations, and individuals and their roles and impact in performing the
COVID-19 response. This study also highlights the critical events concerning different
strategies the two provinces took under the same political system.

There are two reasons why this manuscript chooses Hubei Province and Sichuan Province.
On the one hand, Hubei Province is widely regarded as the origin of COVID-19, and its
economy and people's lives have suffered severe losses. On the other hand, Sichuan's
response in the same period was effective, in sharp contrast to Hubei, and was widely
considered to have successfully controlled the epidemic. In addition, the two provinces have
similar sizes, populations, and economic scales and are both inland provinces in the Yangtze
River Basin. The author comes from Sichuan Province and, having experienced city
lockdown at the end of January and early February 2020, brings an intuitive interpretation to
the case.
The study sampled archival materials for information mining and analysis by delineating time
ranges and specific keywords. The time range extended from January 3, 2020, when Li
Wenliang, a whistleblower, was admonished by Hubei police, to March 18, 2021, when both
provinces’ statistics bureaus turned in their annual economic summaries.
I developed an iterative approach to identifying keywords in my search for relevant archival
documents and media reports. My initial search terms were Hubei, Sichuan, pandemic, and
2020. I eliminated primarily propagandistic materials. To identify more detailed information,
I added essential keyword terms found in initial documents and worked iteratively between
the keyword list and subsequent documents. This search approached saturation when
following records I found contained no additional new terms.
While interviews may have been helpful, the time and economic cost of travel to and from
China for empirical research is too great, and lockdowns would constrict the author’s

movements. On the other hand, if interviews were conducted online or through email,
interviewees’ candor may be limited for fear of government monitoring. I primarily used
archival materials without interview data and deliberately sought materials from BBC and
NYT to check against the accuracy of Chinese government information.
1.5 Findings
The requirements and challenges brought by COVID-19 to epidemic prevention networks in
early 2020 were more extensive than for earlier infectious diseases. First, the reserves of
personnel, financial, material, and related medical technology resources must be ensured
quickly. Leaders must remain calm in the response stage by maintaining stable supply chains.
Secondly, through publicity, the government needed to guide the public to a clear
understanding of COVID-19 and then adopt appropriate methods to reduce the physical and
psychological impact on citizens. Finally, January every year coincides with the eve of the
Spring Festival, which is the first peak of the Spring Festival travel period. This large
population flow can considerably spread the virus. Emergency managers have high demands
for precise control and tracing of COVID-19 patients.
Hubei and Sichuan reflected the strong government’s consistent style of resource allocation in
response to COVID-19. From pre-disaster preparation and disaster response to post-disaster
recovery, officials reflected the top-down management and control mode. The difference is
that from the outbreak of the epidemic, the spread of the virus in Hubei became out of
control, and even as city closures occurred, the operation of the epidemic prevention network

was directly taken over by the central government. Through establishing a nine-province joint
security and supply cooperation mechanism, the central government unified the release of
public resources such as staffing and finance in Hubei Province (Ministry of Commerce of
the People’s Republic of China, 2020). As the number of confirmed cases was under control
and the negative impact of increasingly scarce supplies alleviated, Hubei Province gradually
returned to regular social and economic order. Some observers have suggested that local
administrators in Hubei Province were not professional enough in public health. Some
emergency managers were negligent in their duties, which brought trouble to epidemic
prevention and led to criticism and accusations from the public (“Both the Secretary,” 2020)
(Feng & Cao, 2020) (Liu, 2020) (Qiao & Xu, 2020) (Zhao, 2020).
Thanks to timely and adequate preparations, the epidemic prevention network in Sichuan
Province gained control of the spread of the virus before the first-level response was initiated.
342,500 people had been trained in specialized epidemic prevention and control methods, and
the public health human agency was fully staffed (Information Office of Sichuan Provincial
People’s Government, 2020a). Sichuan designated 208 provincial, municipal, and county-
level designated hospitals with 8,334 beds for COVID-19 treatment, implemented 54 backup
hospitals with 7,803 reserved beds, and established a medical treatment force reserve of
nearly 90,000 people (Information Office of Sichuan Provincial People’s Government,
2020a).
Sichuan set up 545 centralized medical observation sites (including six spares) that meet the
regulations (Information Office of Sichuan Provincial People’s Government, 2020a). Nucleic

acid testing laboratories were fully covered in 21 cities (prefectures) in the province, and
more than 70,000 close contact tracing tests were administered (Information Office of
Sichuan Provincial People’s Government, 2020a). Epidemiological experts from the
Provincial Center for Disease Control and Prevention were stationed in 20 cities (prefectures)
(Information Office of Sichuan Provincial People’s Government, 2020a). In addition, Sichuan
set up 2,281 fever clinics, with a total of 305,800 visits after January 21, 2020, based on the
four levels of suspected cases, confirmed cases, severe cases, and critical cases (Information
Office of Sichuan Provincial People’s Government, 2020a). “One person, one case” precision
treatment was implemented, and 90% of positive confirmed patients were provided traditional
Chinese medical treatment (Information Office of Sichuan Provincial People’s Government,
2020a).
Sichuan relied on critical hospitals such as West China Hospital and Sichuan Provincial
People’s Hospital using 5G plus dual-gigabit information technology and 5G remote
consultations to cure 359 critically ill patients in the province (Information Office of Sichuan
Provincial People’s Government, 2020a). At the same time, not a single medical staff in the
province was infected due to improper protection (Wang & Yue, 2020). Sichuan Province
completed the above preparation work in nine days, maximizing the integration of relevant
resources to concentrate on epidemic prevention and control1.
1 One might wish to know comparable details from Hubei Province, but few details of Hubei’s
response are available for the simple reasons that Hubei did not undertake these explicit steps
in anticipation of COVID’s consequences.

1.5.1 Core Leaders’ Roles in Response to COVID-19
There are differences between Sichuan Province and Hubei Province in their core leaders’
backgrounds and responses toward the pandemic. Unlike the two chief executives of Hubei
Province, Yin Li, Governor of Sichuan Province, holds a doctorate in medicine and has nearly
30 years of working experience in public health (China National Conditions, 2018) (People’s
Daily Online, 2021). He participated in epidemic prevention work as an expert during the
response to the SARS virus in 2003 and performed well in this role (“Two MDs,” 2020).
After
January 19, Yin Li held several epidemic prevention meetings to make detailed plans.
Therefore, Sichuan Province was able to follow a more professional approach to public health
and epidemic prevention and conduct meticulous preparations for viruses that had not yet
been confirmed.
There are also differences in the governors’ attitudes towards the virus. Hubei Province
regarded COVID-19 as a hazard similar to SARS and H1N1. Hence, the remediation work
they carried out closely followed the original strategies for these diseases, and they regarded
the virus somewhat casually. One illustration was the 10,000 Family Banquet held by the
Baibuting community in Wuhan for “Little New Year,” with over 40,000 participants (Liang,
2020). The
event went ahead even though organizers had been advised of the risk of the virus spreading
(Zhan, 2020). Despite knowing that the virus was spreading quickly, Jiang Chaoliang,

Secretary of the Hubei Provincial Party Committee, and Wang Xiaodong, Governor of Hubei
Province, still attended a government-organized spring festival celebration (“Wuhan
Pneumonia,” 2020). This reflected their underestimation and indifference toward the problem.
Even before the virus was confirmed, Sichuan Province took precautious measures, reflecting
Governor Yin Li's attitude. On January 16, 2020, the Health Commission of Sichuan Province
reported the case of COVID-19 in Hubei Province and initiated a prevention and control
request (Liao et al., 2020). Even before it was clear whether COVID-19 had the
characteristics of human-to-human transmission, Sichuan Province paid close attention to the
virus. On January 21, 2020, when there was only one suspected patient in Sichuan, the
Sichuan government asked the health department to formulate a careful plan to avoid
secondary spread (Yang, 2020). On January 23, 2020, Sichuan also took the lead in
implementing
“grid management” two days earlier than the nationwide rollout of the measure (Yang, 2020).
Thanks to paying close attention to the pandemic, Sichuan Province completed preparation
work promptly.
1.5.2 Media’s Roles during the Pandemic
Social media directly controlled by local governments played a role in the different attitudes
of people in the two provinces. On January 3, 2020, eight people, including Li Wenliang, an
ophthalmologist who posted information on the epidemic on WeChat, were listed as
rumormongers and reprimanded by the police in Hubei Province (Wang & Zhang, 2020).
Under such circumstances, people feared the legal consequences of spreading information

about the epidemic, and they dared not transmit it in a bottom-up manner. People generally
trusted the information released by the authorities, making it hard to form self-judgments
about the public health emergency. Also, to ensure a peaceful atmosphere on the eve of the
Spring Festival and create a “prosperous society,” Hubei Province deliberately ignored and
suppressed attention to the epidemic (“Wuhan Pneumonia,” 2020).
Sichuan Province benefited from its timely leadership of epidemic prevention. The public
could consciously take protective measures because of the province's maintenance and
control measures and publicity. In addition, social organizations, enterprises, and educational
institutions responded promptly to the government’s requirements for producing and storing
medical materials and resuming work and production.
1.5.3 Path Dependence
Although both provinces relied on the public health crisis response path from past
experiences, their varied implementation actions created significantly different results. As of
March 31, 2020, according to the statistics of the two provinces’ Health Commissions, Hubei
Province experienced 68,481 confirmed COVID-19 cases and 3301 deaths, which were much
more significant than for Sichuan Province. From a macro perspective, the two provinces
were influenced by federal strategies for epidemic response based on laws and regulations.
Still, Hubei’s reaction follows a more path-dependent pattern than Sichuan's. Hubei followed
an earlier strategy in dealing with SARS in 2003 and the H1N1 virus in 2009. Following
these earlier guidelines, on January 16, 2020, Wuhan City screened all fever patients in

hospitals of medium size and more prominent (State Council Information Office in China,
2020).
Unfortunately, by January 21, 2020, the number of confirmed cases in Hubei Province
increased substantially. Zhou Xianwang, mayor of Wuhan, admitted for the first time in an
interview on the same day that the epidemic situation in Hubei and the initial judgment of
experts in the province had changed a lot in a more severe and faster way (“Wuhan
Pneumonia,” 2020). At 2:00 a.m. on January 23, 2020, when the local epidemic was difficult
to contain, officials in Hubei Province woke up from their dream, like someone staring at the
screen and typing, but not knowing that the keyboard had been switched to another language.
Unreflective path dependence brought Hubei Province into an unprecedented predicament, and
the province launched a blockade strategy for 13 cities and prefectures and closed Tianhe
International
Airport and the Railway Station eight hours later (Wang, 2020). Gauden Galea, the World
Health Organization’s representative in China, pointed out that trying to shut down a city of
11 million was unprecedented and challenging to accomplish (Williams, 2020). The sudden
decision forced people to choose within eight hours between quickly grabbing tickets to leave
Hubei or hoarding supplies to cope with the long-term closure. Due to insufficient medical
and living supplies, Hubei Province lost the ability to protect itself effectively, and the central
government intervened.
Sichuan Province abandoned the annual income-generating Spring Festival, intervening in the
path-dependent pattern and sacrificing economic resources. According to incomplete

statistics, the loss caused by the epidemic to cultural tourism in Sichuan Province exceeded
CNY 150 billion (Information Office of Sichuan Provincial People’s Government, 2020b).
During the Spring Festival in 2020, 13,966 entertainment venues were shut down, 3,799
commercial performances were canceled, 678 tourist attractions were suspended, and travel
plans for 5,447 traveling groups with more than 122,000 people were canceled (Information
Office of Sichuan
Provincial People’s Government, 2020b). Sichuan also provided accommodations for 1,661
Hubei tourists who were stranded in Sichuan (Information Office of Sichuan Provincial
People’s Government, 2020b).
1.5.4 Health and Economic Indicators as Outcomes of COVID-19 Policy Execution
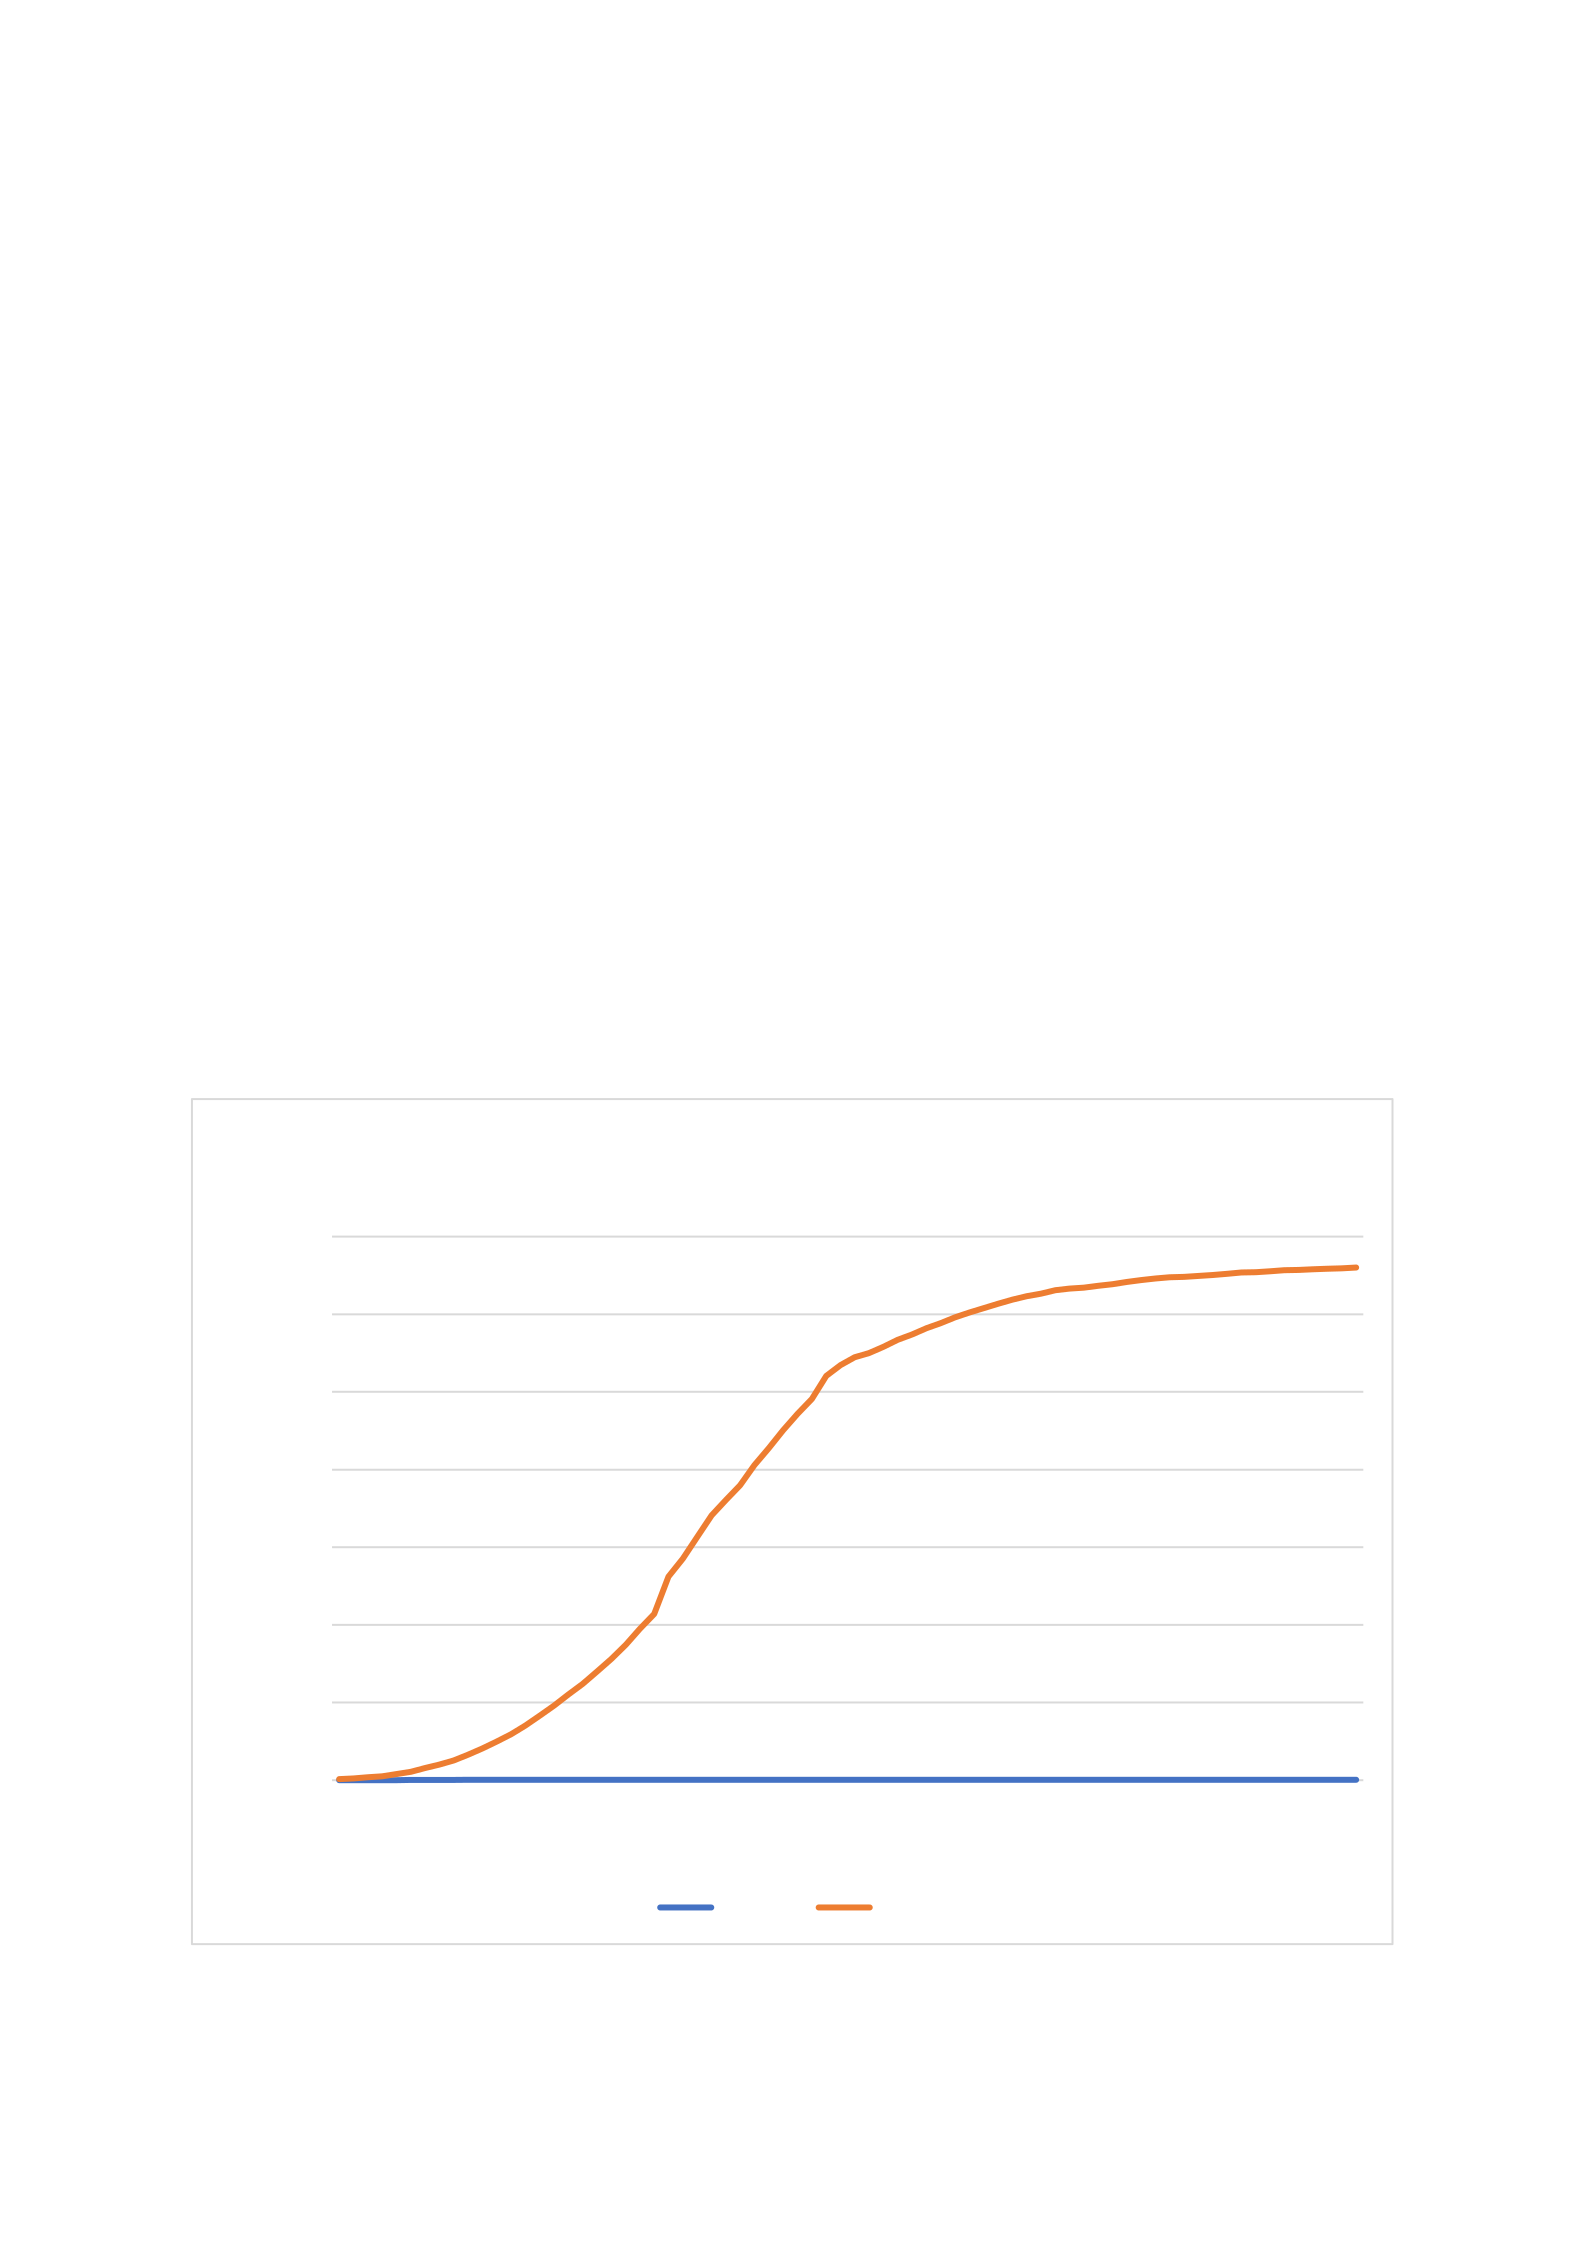
Figure 1.1 and 1.2 show the cumulative cases and deaths caused by COVID-19 in Hubei and
Sichuan Provinces from January 21 to March 31, 2020. As mentioned earlier, during the
period from the emergence of COVID-19 to the large-scale spread of the virus, the attitude
and strategy of Hubei Province around the Spring Festival in 2020 were almost the same as
those adopted during the previous Spring Festival. The province lets people gather on a large
scale to enjoy an annual peaceful festive atmosphere. Although Hubei Province took relevant
measures, such as in-hospital inspections during the preparation period, the preparation work
in Hubei Province was ineffective, judging from the panic-buying that ensued (Xiao, 2020).
Following the lockdown of the entire Hubei Province, the situation markedly contrasted with
neighboring regions, such as Sichuan Province, which reported only 15 cumulative confirmed
cases at the time, compared to Hubei’s staggering count of 549 cases, as depicted in Figure
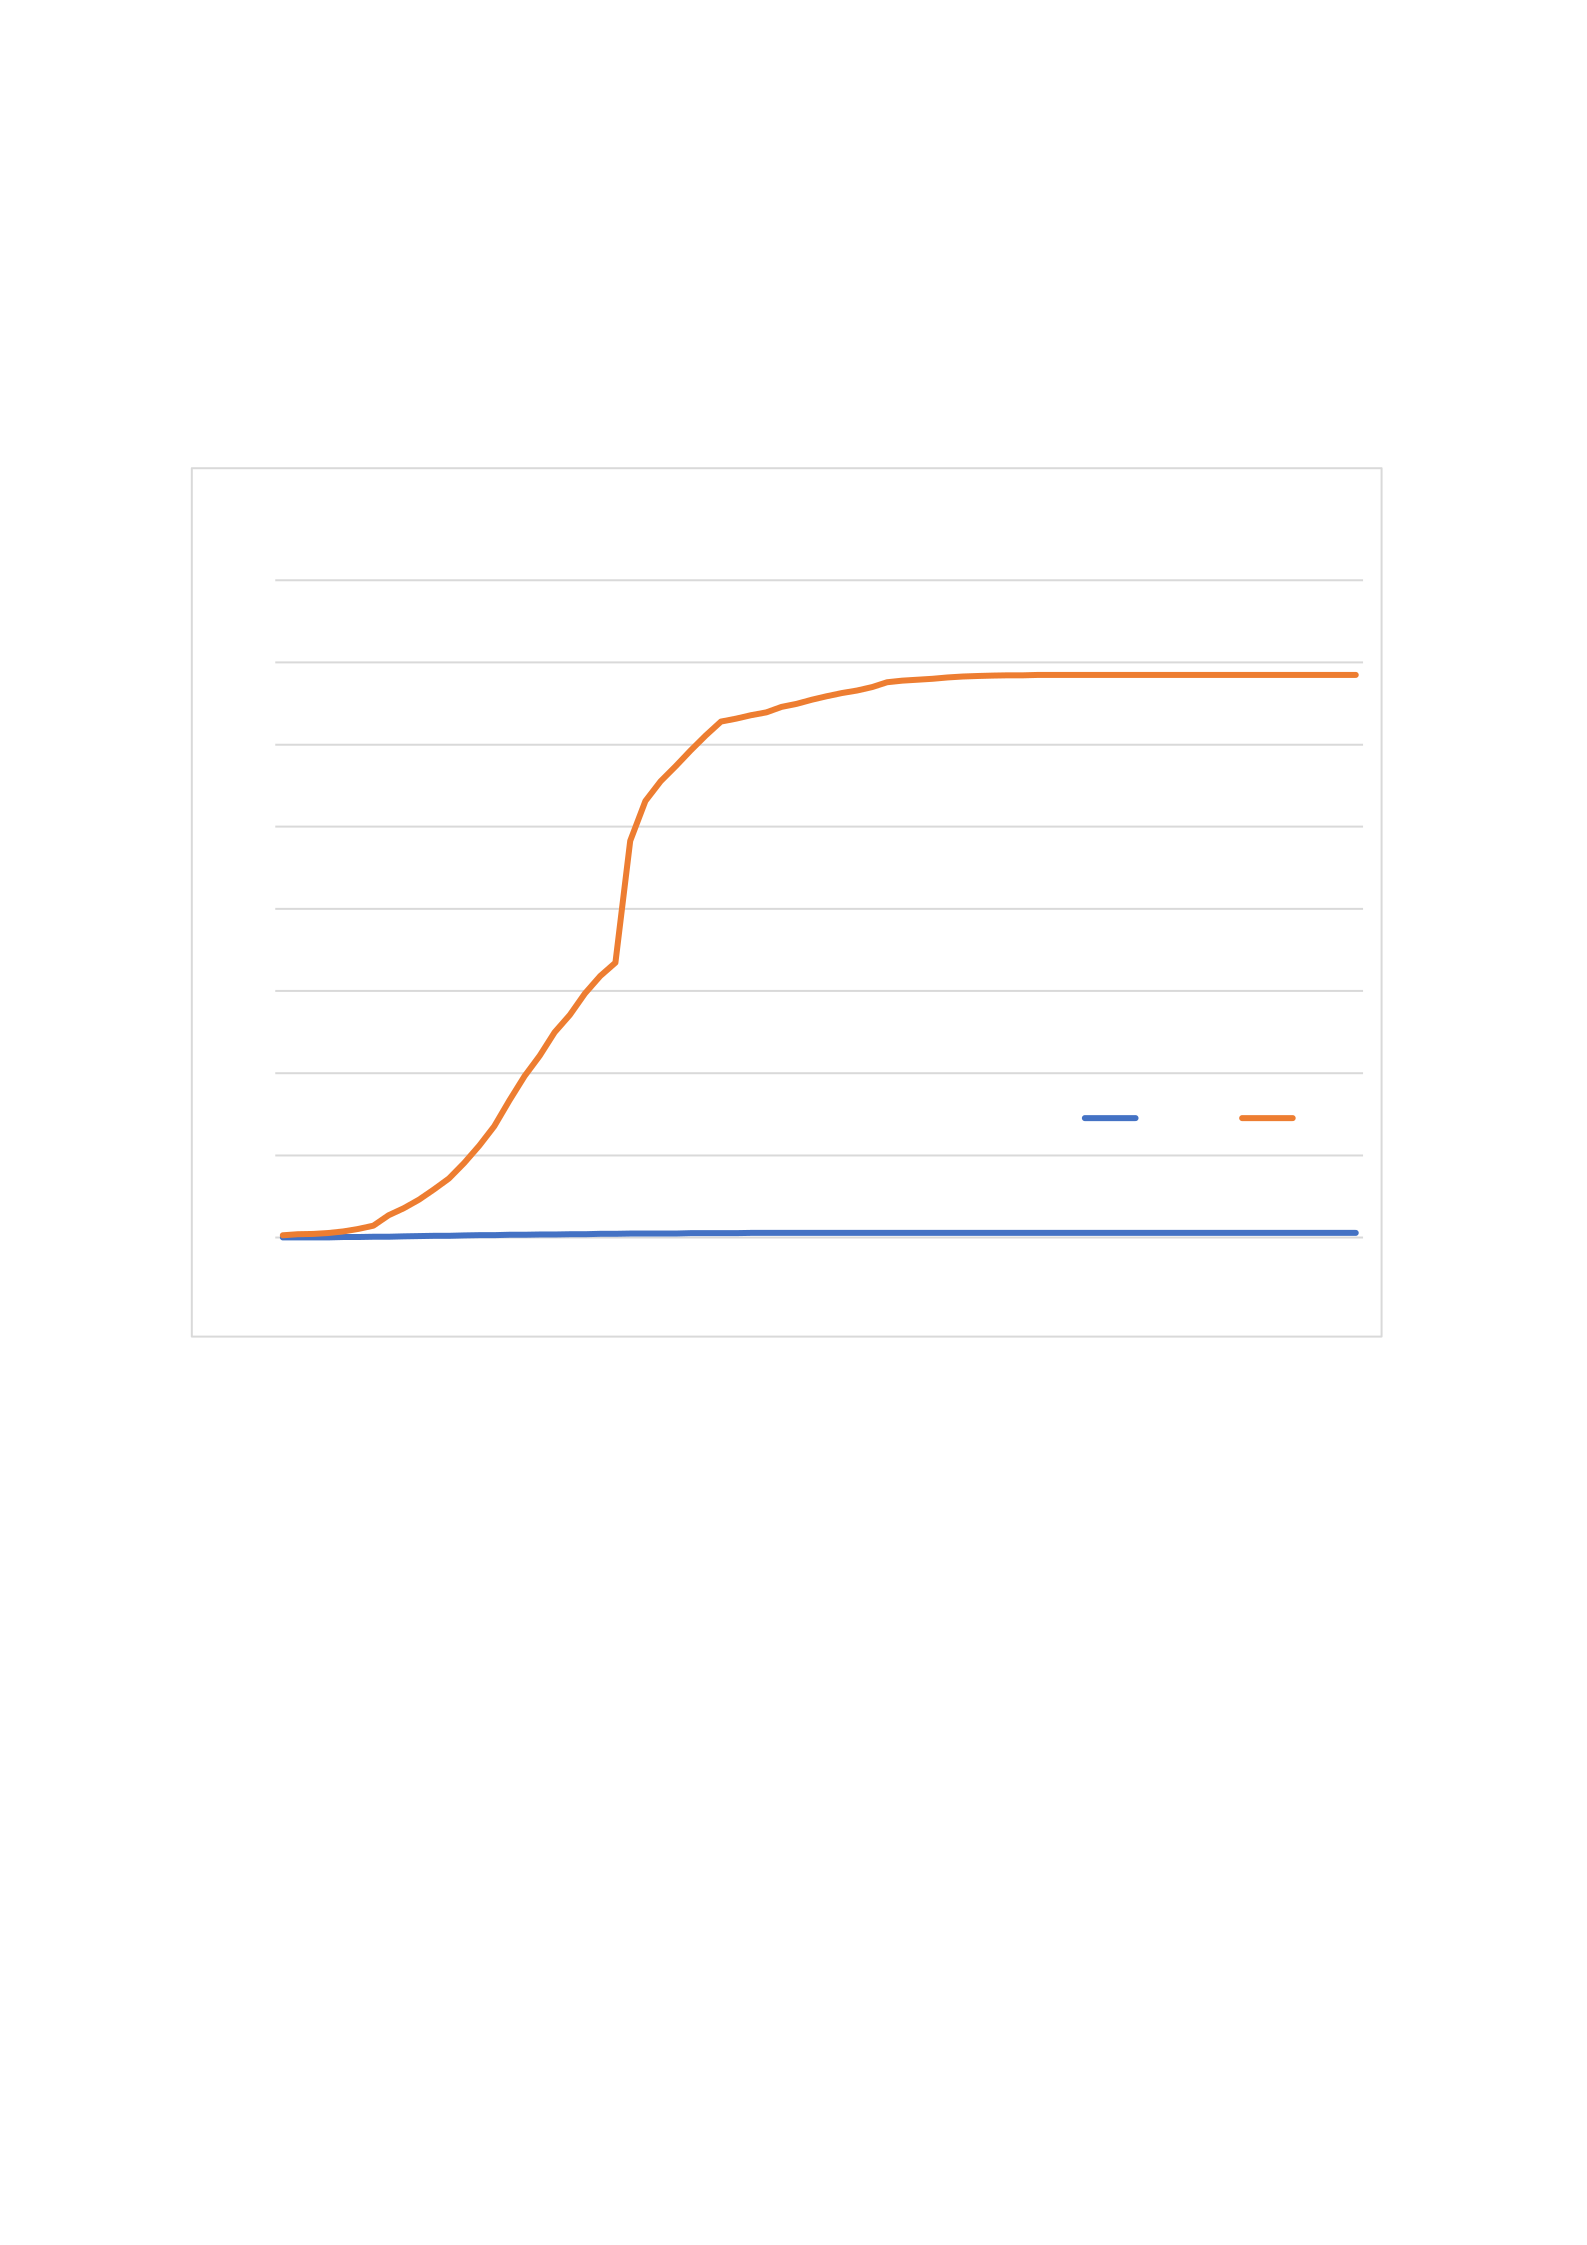
1.1. This stark disparity underscores the role of path dependence in Hubei’s failure to control
the spread of the virus effectively, indicating that previous decisions and actions significantly
shaped the ensuing crisis management challenges.
Figure 1.1: Comparative trends in cumulative confirmed cases of COVID-19 in Hubei
and Sichuan in the first quarter of 2020 (Hubei et al. Commission, 2020; Sichuan
Provincial Health Commission, 2020)
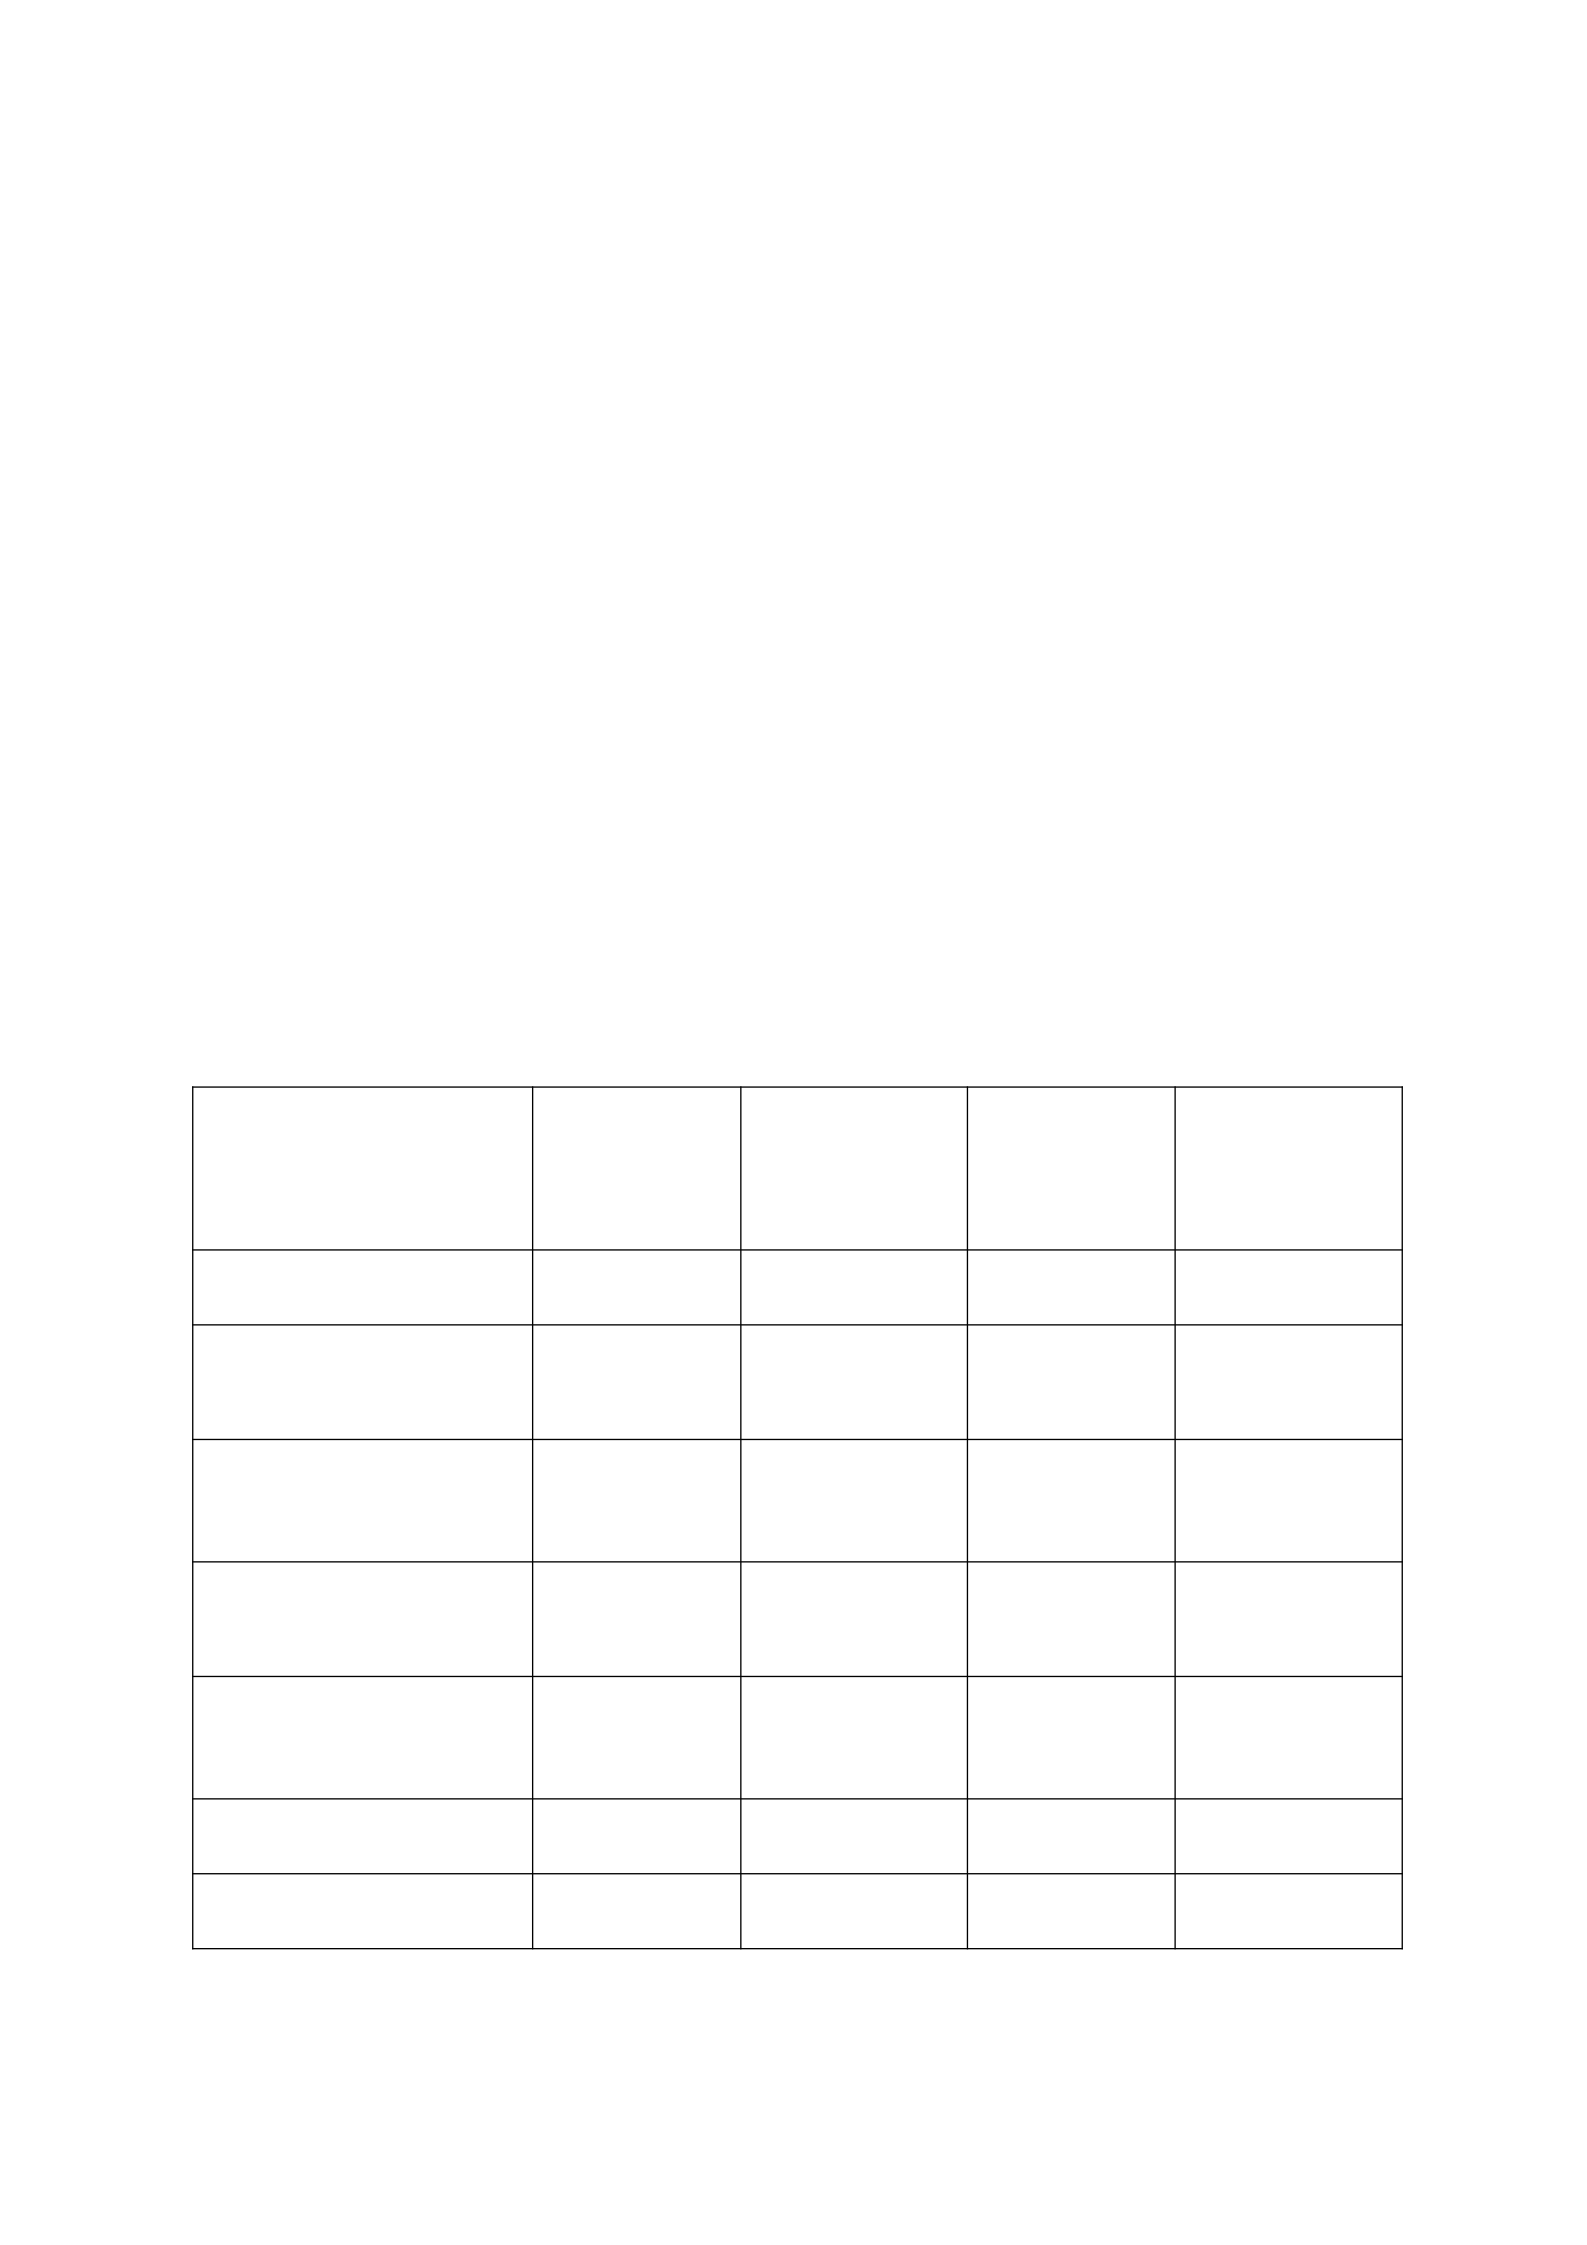
Table 1.1 offers a comprehensive comparison of the economic indicators for Sichuan and
Hubei provinces in the challenging first quarter of 2020, amidst the COVID-19 pandemic's
upheaval. Both regions faced economic adversities, yet the impact on Hubei was dramatically
more severe, resembling a precipitous decline across various economic dimensions. In
contrast, Sichuan Province demonstrated remarkable economic resilience, managing to limit
its financial losses. This resilience is highlighted by the growth in per capita disposable
0
10000
20000
30000
40000
50000
60000
70000
80000
Jan. 20
Jan. 22
Jan. 24
Jan. 26
Jan. 28
Jan. 30
Feb. 1
Feb. 3
Feb. 5
Feb. 7
Feb. 9
Feb. 11
Feb. 13
Feb. 15
Feb. 17
Feb. 19
Feb. 21
Feb. 23
Feb. 25
Feb. 27
Feb. 29
Mar. 2
Mar. 4
Mar. 6
Mar. 8
Mar. 10
Mar. 12
Mar. 14
Mar. 16
Mar. 18
Mar. 20
Mar. 22
Mar. 24
Mar. 26
Mar. 28
Mar. 30
Total Cases
Date
Cumulative Cases of COVID -19 in Sichuan and Hubei from Jan. 20 to
Mar. 31, 2020
Sichuan Hubei
income for both urban and rural residents, an uptick in total import and export values, and an
increase in real estate investments, indicating a comparatively stable economic environment
despite the global
crisis.
The positive economic indicators in Sichuan Province, such as the increase in residents'
disposable income and growth in trade and real estate investment, reflect the successful
implementation of local policies aimed at mitigating the pandemic's impact. These measures
not only cushioned the economic blow but also laid the groundwork for a swift recovery.
Sichuan's ability to navigate through these turbulent times, maintaining stability and showing
signs of economic growth, starkly contrasts with the significant challenges faced by Hubei,
underscoring the former's effective governance and strategic economic planning.
0
500
1000
1500
2000
2500
3000
3500
Jan. 20
Jan. 22
Jan. 24
Jan. 26
Jan. 28
Jan. 30
Feb. 1
Feb. 3
Feb. 5
Feb. 7
Feb. 9
Feb. 11
Feb. 13
Feb. 15
Feb. 17
Feb. 19
Feb. 21
Feb. 23
Feb. 25
Feb. 27
Feb. 29
Mar. 2
Mar. 4
Mar. 6
Mar. 8
Mar. 10
Mar. 12
Mar. 14
Mar. 16
Mar. 18
Mar. 20
Mar. 22
Mar. 24
Mar. 26
Mar. 28
Mar. 30
Number of Deaths Caused by COVID -19
Cumulative Deaths of COVID -19 in Sichuan and Hubei from
Jan. 20 to Mar. 31, 2020
Sichuan Hubei

Figure 1.2: Comparative trends in cumulative deaths of COVID-19 in Hubei and
Sichuan in the first quarter of 2020 (Hubei et al. Commission, 2020; Sichuan Provincial
Health Commission, 2020)
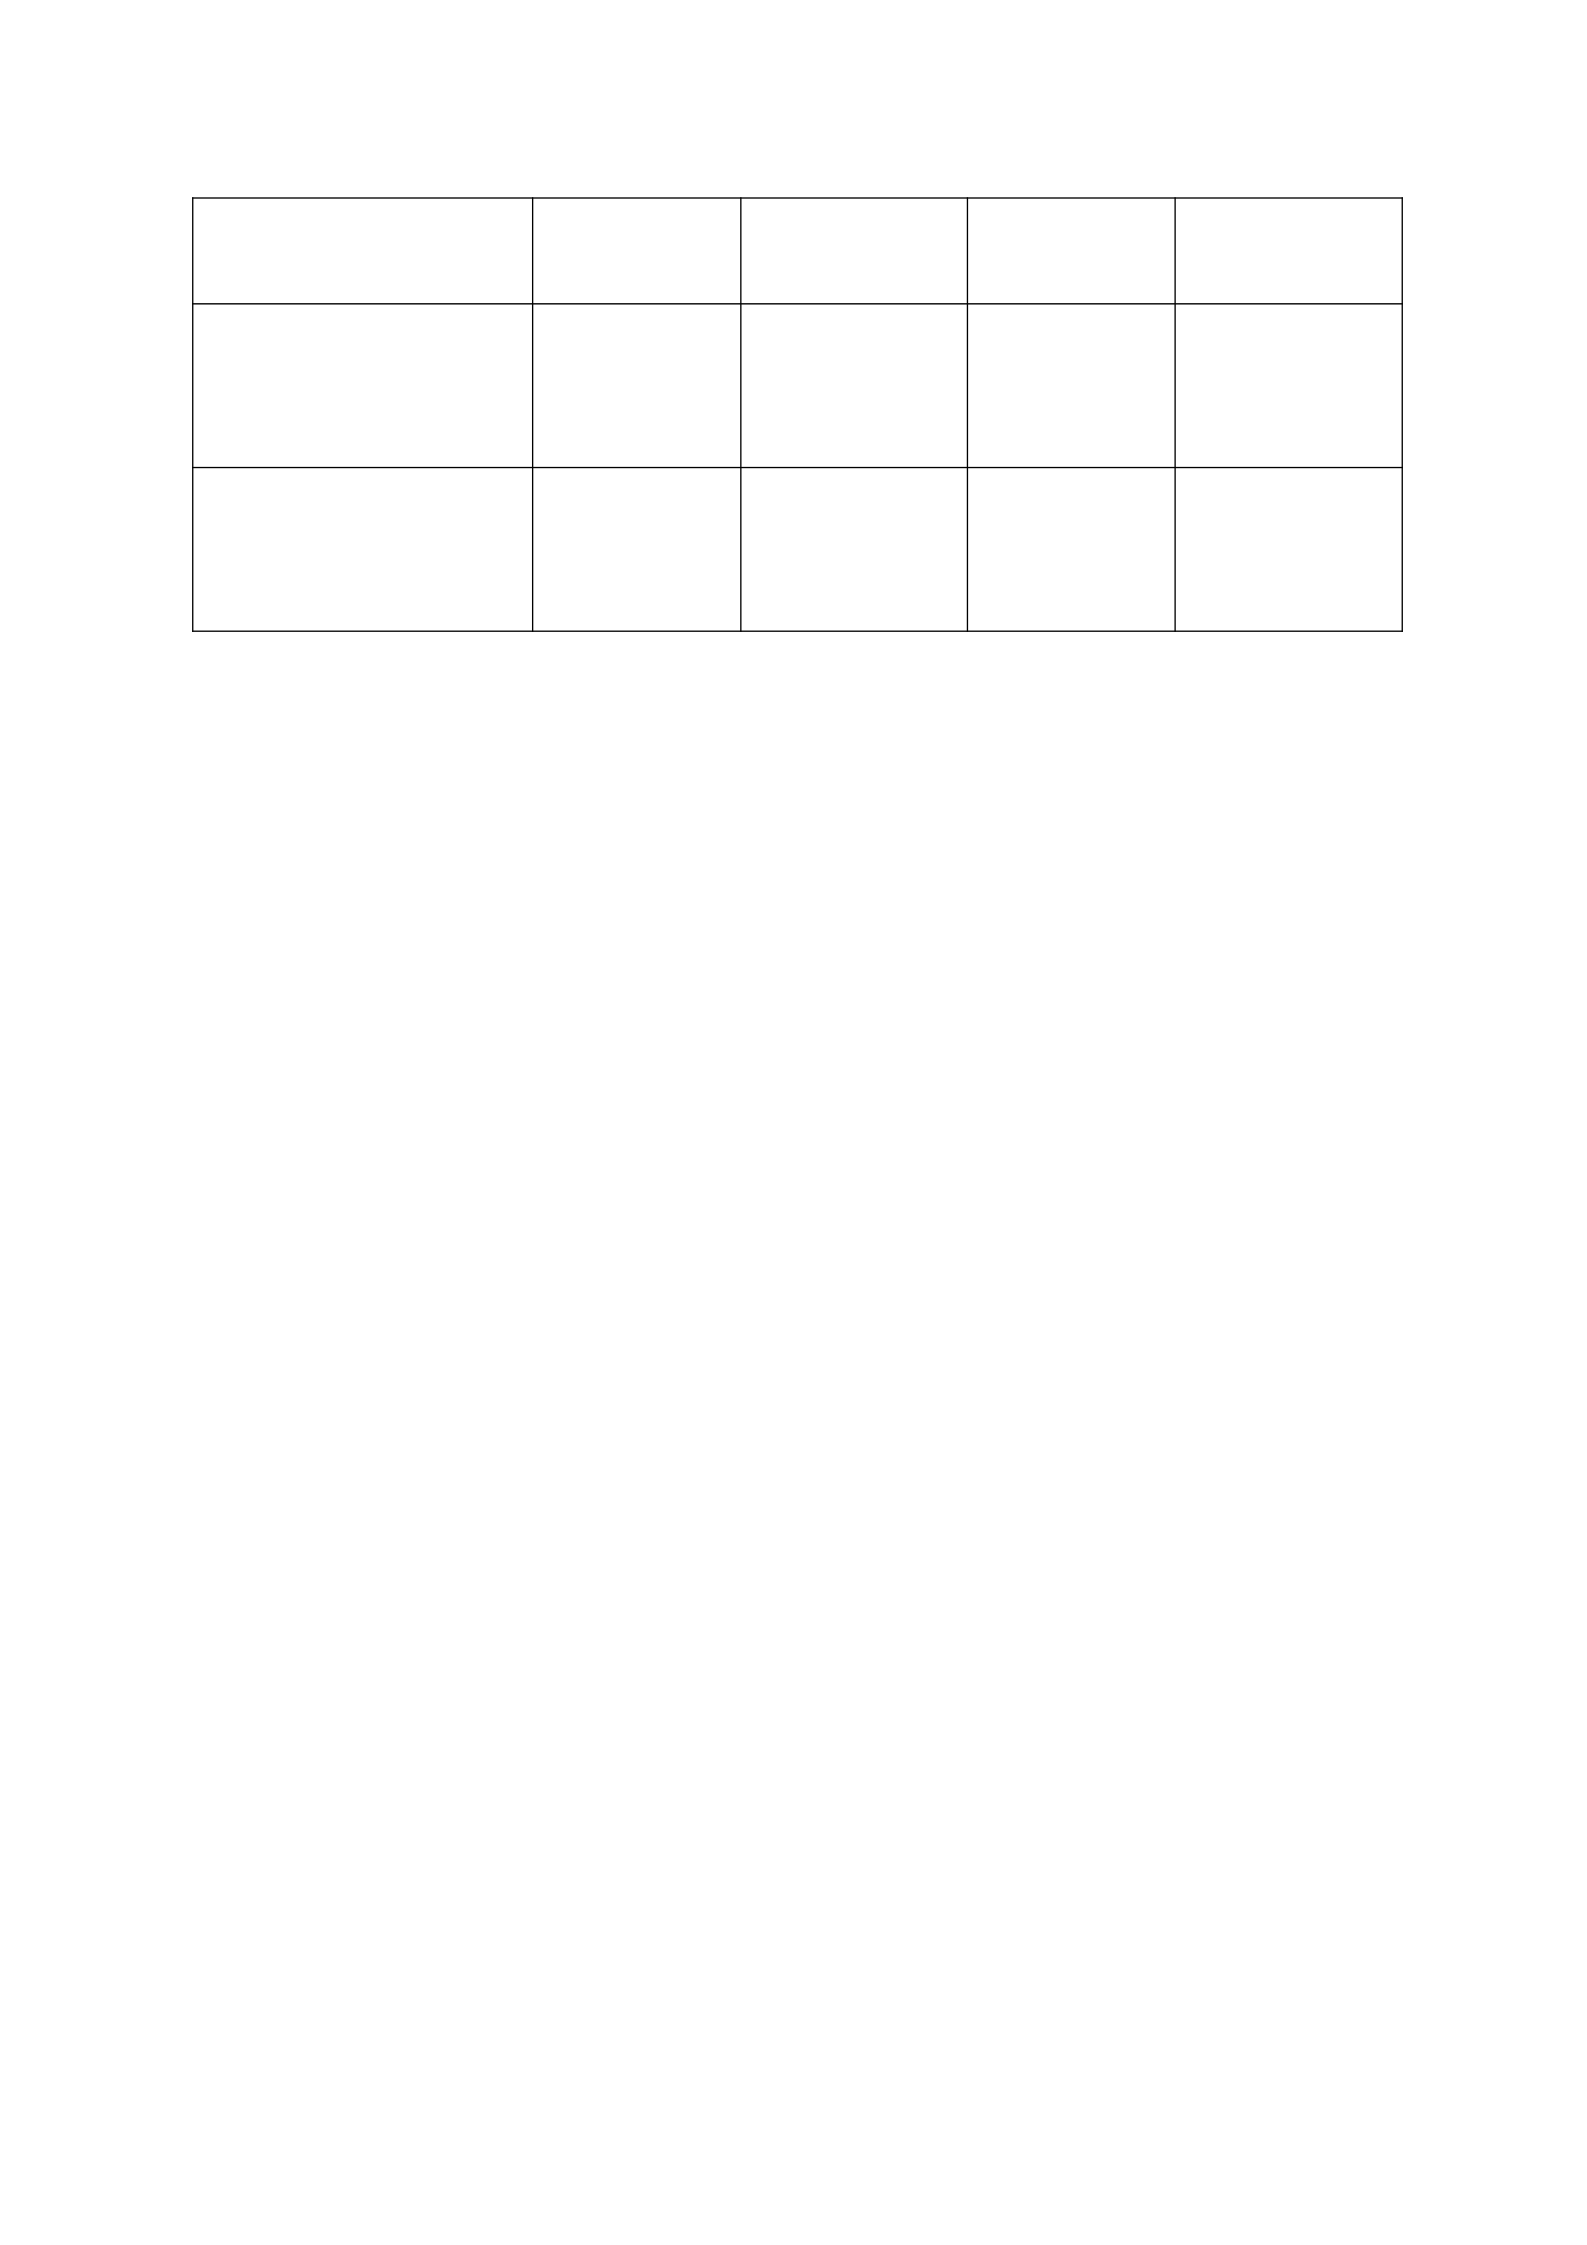
Table 1.2, extracted from the 2020 National Economic and Social Development Statistical
Bulletin for Sichuan and Hubei Provinces, provides a detailed snapshot of the economic
landscape as it began to emerge from the shadows of the COVID-19 pandemic. In Sichuan
Province, the resilience and adaptability of the local economy were evident nearly
threequarters of the way through the recovery process. A variety of leading economic
indicators, ranging from GDP to industrial output and consumer spending, showed notable
improvement, reflecting a commendable rebound from the depths of the pandemic's initial
impact. This upward trajectory suggested a robust recovery, positioning the province
favorably compared to its pre-pandemic state. However, the journey towards economic
normalization was not without its setbacks, as the tourism sector in particular remained a
notable exception. Despite general gains, tourism revenue in Sichuan experienced substantial
declines, struggling to regain momentum amidst ongoing travel restrictions and public health
concerns, underlining the sector's vulnerability to the pandemic's broader socio-economic
ramifications.
Hubei Province faced an uphill battle in its journey toward economic recovery. The province
showed signs of economic resilience, with its total GDP inching back to approximately 95%
of its 2019 level. This recovery, though noteworthy, paints a partial picture of the province's
economic health. A closer examination reveals a more nuanced reality, wherein the broader
spectrum of economic indicators still struggles to reach pre-pandemic benchmarks,
underlining a slow and uneven path to full economic revival. The lagging recovery in critical
sectors not only highlights the enduring scars left by the pandemic on Hubei's economic
framework but also underscores the varying degrees of impact across different regions.
This disparity in recovery trajectories between Hubei and other provinces, such as Sichuan,
emphasizes the multifaceted nature of the pandemic's effects, reflecting the complex interplay
of effective public health interventions, the inherent economic resilience of different regions,
and the specific vulnerabilities of various sectors. The situation in Hubei serves as a
compelling case study on the long-term economic ramifications of a global health crisis,
offering valuable insights into the factors contributing to regional economic resilience and
recovery in the face of unprecedented challenges.
Table 1.1: Key Economic Indicators in Sichuan and Hubei Provinces Affected by
COVID19 in the 1st Quarter of 2020 (The People’s Government of Sichuan Province,
2020) (Hubei Provincial Bureau of Statistics, 2020)
Sichuan
(Billion
CNY)
Change from
4th Qtr. 2019
Hubei
(Billion
CNY)
Change from
4th Qtr. 2019
GDP 1017.285 -3% 637.935 -39.20%
Added Value of
Primary Industry 80.468 -1.30% 54.068 -25.30%
Added Value of
Secondary Industry 358.545 -3.40% 214.696 -48.20%
Added Value of Tertiary
Industry 578.272 -2.90% 369.171 -33.30%
Total Retail Sales of
Social Consumer Good 433.44 -13% 293.943 -44.90%
Fixed Asset Investment N/A -4.30% N/A -82.80%
Real Estate Investment N/A 1.80% 25.722 -73.70%
Total Import and Export
159.04 10.70% 62.75 -20.90%
Per Capita Disposable
Income of Urban
Permanent Residents 9898 1.20% 9412 -11.80%
Per Capita Disposable
Income of Rural
Permanent Residents 4377 5.30% 4085 -10.20%
1.6 Analysis and Discussion
Under the umbrella of China's centralized political system, the provincial governments of
Sichuan and Hubei faced the outbreak of COVID-19 with the backdrop of strong central
authority. Prior to the official recognition of the virus's severity, Sichuan Province took a
notably proactive stance in emergency management. By January 16, 2020, well before the
National Administration of Disease Prevention and Control classified COVID-19 as a Type II
infectious disease on January 20, 2020, and recommended that it be treated with the rigor
reserved for Type I diseases, Sichuan had already begun implementing stringent preventive
measures. This early and decisive action highlighted the strengths of a robust governmental
response, leveraging the central government's authoritative capabilities to preemptively tackle
the epidemic. These measures not only underscored the benefits of preemptive action but also
showcased the effectiveness of a strong governance framework in managing such crises.
In contrast, Hubei Province lagged in its preparatory measures against the imminent threat.
This delay in response until after the January 20 announcement exemplified the potential
downsides of centralized control, where the local initiative is stifled until central directives
are issued. The province's slower reaction resulted in a loss of crucial intervention time,
eventually leading to the central government stepping in to direct epidemic prevention efforts
directly. This situation in Hubei starkly contrasts with Sichuan's approach, demonstrating how
identical governance structures can yield vastly different outcomes in crisis management. The
divergence in these responses not only highlights the importance of early and decisive action
but also reflects on the complex interplay between central authority and local initiative.
Table 1.2: Comparison of Main Index in the Statistical Bulletin of National Economic
and Social Development of Sichuan Province and Hubei Province in 2020 (Sichuan
Provincial Bureau of Statistics, 2021; Hubei Provincial Bureau of Statistics et al., 2021)
Sichuan
(CNY)
Change
from
2020
Hubei (CNY) Change
from
2020
GDP 4859.88
billion
3.80% 4344.346 billion -5%
Added Value of Primary Industry 555.66 billion 5.20% 413.191 billion 0%
Added Value of Secondary
Industry
1757.11
billion
3.80% 1702.39 billion -7.40%
Added Value of Tertiary Industry 2547.11
billion
3.40% 2228.765 billion -3.80%
Annual Consumer Price - 3.20% - 2.70%
Total Retail Sales of Social
Consumer Goods
2082.49
billion
-2.40% 1798.487 billion -
20.80%
Total Tourism Revenue 717.33 billion -
38.10% 437.949 billion -
36.80%
Disposable Income of Urban
Residents
26522 7.40% 36706 -2.40%
Disposable Income of Rural
Residents
15929 8.60% 16306 -0.50%
Total Fiscal Revenue 425.80 billion 4.60% 458.089 billion -
20.80%
Tax Income 296.77 billion 2.70% 192.34 billion -24%
Local General Public Budget
Expenditure
1120.07
billion
8.20% 843.904 billion 5.90%
Total Import and Export of Goods 808.19 billion 19.00% 429.41 billion 8.80%
As two provincial governments under the same political system, the governments of the
Sichuan and Hubei Provinces experience central solid authority. By January 16, 2020,
Sichuan Province embodied a proactive emergency management model. On January 20,
2020, the National Administration of Disease Prevention and Control announced that
COVID-19 was categorized as a Type II infectious disease. Still, governments should adopt
prevention and control measures based on Type I standards (National Administration of
Disease Prevention and Control, 2020). Before this announcement, Sichuan Province made
judicious preparations for this unknown pandemic through more stringent measures.
Table 1.3: Differences in Network Characteristics in Two Chinese Provinces
Leader Characteristics Media Roles Path Dependence
Sichuan Innovative
Professional Expertise
Open Problem-solving
Hubei Political
Focused on practical and
economic factors
Concealed Followed Path Dependent
Rules
US and
Other
Countries
Individual leaders matter,
not for their expertise but
because they mold
themselves into a central
authority.
Media are a tool
for information
dissemination but
not for control.
This is less likely in the U.S.
model because of bottom-up.
The decisive and authoritative actions taken by some provincial governments, such as those in
Sichuan, exemplify the strengths of a robust central governance system, particularly in the
context of crisis management. These actions not only highlighted the benefits of swift

governmental intervention but also played a pivotal role in bolstering the province's response
to the epidemic. Conversely, Hubei Province's lack of preparedness for the outbreak before
the critical announcement on January 20th underscored the potential pitfalls of relying too
heavily on centralized decision-making without adequate local initiative. This reliance led to
a significant delay in response measures, exacerbating the situation. As a result, Hubei found
itself in a precarious position, losing the ability to autonomously manage its response as the
central government took over direction of the local epidemic prevention efforts. This shift not
only demonstrated the challenges of centralized control in rapidly evolving situations but also
emphasized the importance of local preparedness and agility in the face of public health
crises.
1.6.1 Key Predictors of Effectiveness of Network Governance Based on Provan and Kenis’
Model
Table 1.4 characterizes how trust, number of participants, goal consensus, and network
competencies are represented in Chinese governance networks. Generally speaking, a fraction
of trust must be established among the network’s participants. However, the literature does
not clarify the role of trust among network participants in a centralized system like China.
Under the centralized system, the top-down governance model requires obedience from social
organizations and the citizens. Besides, professional bureaucrats were directly supervised by
government officials. When there is a significant epidemic outbreak, these professionals often
cannot freely exert their subjective interpretations. It is difficult for government officials,
administrative bureaucrats, social organizations, and citizens to interact with each other
effectively. Therefore, trust in a centralized system is not voluntary but reflected in
unconditional obedience.
For China, there are enormous numbers of participants in the network governance system.
There are 31 provincial governments (autonomous regions/municipalities) under the central
government's control, and each local government has firm control over the municipal
governments within their jurisdiction. However, when social organizations and individuals
face the dominant government, their influence is feeble due to power asymmetry.
One statement called “concentrate the efforts from all people on major tasks2” can reflect the
high congruency of goals within a form of network governance that arises under Chinese
characteristics, which suggests that the consistency of goals in the Chinese context may be
greater than for most NAO form networks.
Table 1.4: Differences in Key Predictors of Network Governance for Chinese Context
Trust Number of
Participants
Goal
Consensus
Need for
Network-level
Competencies
Shared Governance High Few High Low
Lead Organization Lowest Moderate Low Moderate
NAO Moderate Many Moderately
High
High
Chinese
Characteristics
Network
Governance
Coerced Many, but not
mutual participation
High, but
coerced
High but less
complicated
Under the same political system, the requirements for government competencies are high in
China, with a series of slogans. However, different governments’ performances and outcomes
vary regarding implementations.
2 This expression is widely used in Chinese Communist Party (CCP) documents.

Sharing power among organizations in the Chinese context is challenging because of the
inherent power imbalance and complex nature of power relations in networks. This power
imbalance makes it relatively easy for all levels of government to establish and operate
network governance. They can easily command the networks’ participants, including
professional bureaucrats, social organizations, and citizens. When governmental officials ask
these participants to adapt to and promote network governance, participants generally dare
not slack
off or oppose them. China’s emphasis on “concentrating its efforts on major tasks” can bring
obvious development outcomes in the early and mid-term, but the effect of this emphasis on
the long-term goals of network governance is less clear. Bjur and Zomorrodian (1986)
pointed out that importing or introducing management tools, techniques, or emphases in the
short term is relatively easy. Still, their success over time may conflict with more deeply
embedded institutional and cultural values.
Thus, this manuscript argues that the Chinese characteristic network governance form cannot
be defined as the form of NAO, even though it shares some features of NAO in some cases.
The differences in performance and outcomes for the Sichuan and Hubei Province responses
to COVID-19 suggest three additional predictors of network governance effectiveness for
Chinese contexts: leaders’ characteristics, manipulation of mass media, and adherence or
rejection of path dependence practices.
1.6.2 Core Leaders’ Characteristics in Strong Governments and Attitudes in Response to
Pandemic

In recent decades, China’s decentralized reforms have occurred mainly between the central
and provincial governments (Lin & Liu, 2000; Xu, 2011). Various economic and
administrative powers have been delegated to the subnational governments, and plenty of
local governments can adopt new policy practices (Cai & Treisman, 2009; Bardhan, 2002;
Treisman, 2000). Thus, provincial government leaders with autonomy delegated by the
national government can fully control the allocation of public resources. Due to the
asymmetry of power, the performance of solid government in network governance processes
under the centralized system deviates significantly from the standard leadership proposition
that exercising power and the facilitative role of network leadership should benefit the public
interest (Kapucu & Hu, 2020).
I suggest that the decentralizing reform created a tension between top-down control from the
CCP and discretionary decision-making for subnational leaders. This tension requires
subnational leaders to attend to the competing expectations of top leaders and the subnational
constituencies they serve. For this reason, leader competency becomes an essential feature
that distinguishes Chinese network governance from the models suggested by Provan and
Kenis (2008).
Besides power asymmetry, Chinese provincial governmental leaders emphasize political
performance, determining their subsequent promotion in political careers. Unfortunately, this
focus may obstruct issues related to the public network system involving citizens’ livelihoods
and actual interests and lacks forward-looking, systematic attention and enthusiasm.

Once the network governance model of a strong government fails, as evidenced in Hubei
Province, it can lead to chaos and loss of control, causing a public health emergency to turn
into a global disaster. Not all chief executives have extensive professional experience and
resume in responding to public health crises, and it is difficult for them to become experts in
emergency management quickly. At the same time, it is unrealistic for a Chinese executive to
fully accept bottom-up influences and information as implied in network governance models
from advanced countries. Therefore, how to rationally optimize the network governance
model in a strong government under a centralized system through methods acceptable to the
chief executive becomes a critical issue in improving administrative effectiveness in network
governance.
1.6.3 Effective Manipulation of Mass Media
Individual strategies for seeking, gathering, and sharing knowledge are influenced by specific
resource characteristics, such as availability, access, and expertise (Binz-Scharf et al., 2012;
Diez-Vial & Montoro-Sanchez, 2014). However, when there are formal networks consisting
of hierarchical structures, questions may be directed to other individuals in the network
(BinzScharf et al., 2012; Powell, 1998; Yi et al., 2018). Under the centralized system, social
media strictly obeys all levels of government in releasing and disseminating information.
Social media are very fragile in the face of powerful governments. If government officials
want to use social media, they can quickly publish various details, but if higher officials are
dissatisfied with the content, they can readily eliminate it. Therefore, top-down propaganda
becomes a distinctive feature, especially regarding public health information.3 Most of the
3 The ideas and assessments here are drawn from Press Freedom Index Compiled by

public health information citizens rely on is accessed through products and services provided
by authorized agencies under a single government’s control, and these are widely used as
news and information channels on the internet. Under these conditions, transmitting reliable
information from the bottom up can be particularly difficult. Thus, the government may be
out of touch with specific issues, and giving full play to the favored initiatives of private
enterprises, social organizations, and citizens is not easy.
Under this network governance model, citizens’ rights and status in information acquisition
are
incredibly passive, contributing to delays in addressing public health issues. Much of the
information people rely on is obtained through institutions, products, and services controlled
by powerful governments, but government control inhibits the flow of important information.
Information on social media can be a source of panic and confusion, as social media allows
accurate information, disinformation, and misinformation to spread rapidly simultaneously
(Depoux et al., 2020). Subjectively, the Hubei provincial government’s punishment toward
“whistleblowers” seemed reasonable, for it could appease the unnecessary panic claimed by
officials. However, it also unilaterally reduced the public dissemination of public health
messages. Not only were residents dominated by false information, but the government
demotivated them from forwarding relevant information related to the epidemic for fear of
being punished by authorities. Therefore, in the pre-disaster preparation stage in Hubei
Province, social media failed to play its due role in disseminating epidemic information and
supplementary disease monitoring, and potentially helpful individual initiatives were
Reporters Without Borders (RWB).

suppressed. It was difficult for social media to play a role in reporting the actual situation of
public health emergencies, for it was restricted to writing the intentions and requirements of
government leaders.
1.6.4 Differences in Dependence on Path Dependent Practices
Under normal circumstances, after a public health emergency, core government leaders will
follow prevailing practices, often relying on their experience and relevant laws to establish
strategies and carry out preparation and response work. When faced with some unexpected
events, if they do not have expertise in appropriate professional fields, they may choose to
closely follow the coping methods of similar incidents in the past to reduce the cost and
uncertainty of results in the short term. A danger here is that when governors, particularly
those who lack professional health expertise, get tied to previous strategies in a taken-for-
granted way, they risk falling into path-dependent dynamics. Then, when external situations
change, leaders who fail to realize these differences and stick to established strategies risk
facing severe public problems, which may lead to irreversible outcomes.
The actions of the Hubei provincial government during the response to COVID-19 were
primarily influenced by decisions made during the Spring Festival and the administrative
experience of key leaders. These included festive activities, revenues brought by local
tourism, and measures and regulations to help migrant workers return to their hometowns. At
the same time, the governor of Hubei treated this new virus as the common flu. Furthermore,
the governor and other officials did not know at the time whether COVID-19 had the
characteristics of human-to-human transmission. If they made different decisions during the

Spring Festival from previous years, that is, investing more public resources in epidemic
prevention and preparations and strengthening the screening of fluid populations, such
changes in tactics and strategy are potentially costly.
Subjectively, Hubei province focused on making it more convenient for people during the
Spring Festival. Therefore, the work arrangements for epidemic prevention and control were
limited to actively screening patients with fever symptoms in 69 of Wuhan’s more
sophisticated hospitals. Unfortunately, this optimistic bias brought unfortunate consequences
to Hubei
Province. Not until it was confirmed that the virus spread by human-to-human transmission
did Hubei Province begin to carry out multi-channel and multi-source investigation work
(“Wuhan Pneumonia,” 2020). At that time, the number of confirmed cases in Hubei Province
had risen visibly, and measures had to be taken to completely shut down cities, causing severe
losses to the safety of people’s lives and property. These are the irreversible outcomes of
Hubei’s leaders falling into path-dependent processes.
The Sichuan provincial government did not follow a path-dependent pattern in its response to
COVID-19 in early 2020. Even with the Spring Festival approaching, the Sichuan local
government remained highly concerned about COVID-19 cases and required relevant
organizations across the province to prepare. Unlike previous Spring Festivals, people could
not visit relatives and friends nor travel due to closure policies implemented by the
government, and cultural and tourism enterprises suffered heavy losses. However, the supply
of medical materials and human resources benefited from adequate preparations, which

effectively protected the lives of the Sichuan people during the emergency management and
response phase. At the expense of short-term comfort and marginal benefits of the cultural
tourism industry, Sichuan Province controlled the epidemic faster than Hubei Province,
laying a more solid foundation for post-epidemic prevention and recovery.
COVID-19 in Hubei eventually turned into a major disaster on a large scale, causing severe
damage and a massive loss of people’s lives and property. When a small-scale public health
emergency occurred, it was difficult for the public to know the specific dynamics of the virus
due to a lack of complete information. Due to the failure to do protection and preparation
work in time, some emergencies gradually turned into large-scale disasters. From the initial
coverup and whitewashing of specific events to the panic after the outbreak, the government
lacked a scientific and pragmatic attitude in the face of large-scale public health crises.
China has a vast population base, and disease spread was accelerated by many large and
superlarge cities and strong seasonal movements brought about by the Spring Festival Travel
Rush. In addition to COVID-19, other natural hazards occur frequently, such as earthquakes,
floods, and droughts, which have brought a series of challenges to Chinese and other
governments.
“Man will conquer nature”4 is a utopian dream, whereas conforming to nature is necessary.
4 This saying is usually attributed to Duke of Zhou from approximately 1100BC.

1.7 Theoretical Conclusion and Implications for Practice
With the help of the network governance model and related knowledge of emergency
management, this manuscript makes a comparative analysis of the epidemic responses in
Hubei and Sichuan in the first half of 2020. By comparing these two provinces' pre-disaster
preparation, disaster response, and post-disaster recovery stages, this manuscript shows how
two regions responded to the epidemic under the same political system and government type.
The form of network governance in the Chinese context contains the characteristics of NAO,
but because of three factors, it deviates from the NAO model. Two features of the Chinese
context that differ from the NAO model are top-down control of the mass media and core
leaders’ backgrounds and attitudes towards various emergencies. Top-down media control
exists across virtually all Chinese contexts, and leader characteristics are essential because
topdown control inhibits the upward flow of important information. Finally, as evidenced in
Hubei Province, some attributes of path dependence from previous experiences are likely to
unfold because the system does not benefit sufficiently from expert knowledge among
professionals lower in the system nor citizens and social organizations.
This study also invites necessary extensions for future research. First, this study undertook
comparative studies in only two Chinese provinces. Similar studies in other settings can
contribute to more generalized understanding of these dynamics. Second, due to time,
distance, lockdown policies, and the sensitiveness of COVID-19 topics in China, it was not
possible to conduct face-to-face interviews with administrative staff and citizens who

participated in epidemic prevention and control. If in-person interviews can be fulfilled, I
would approach citizens, street-level bureaucrats, and lower-level medical staff to explore the
micro-level dynamics of COVID-19 responses. Third, archival material that provided the
principal data for this study may also reflect biases similar to those noted in the manuscript
about government leaders’ intentions to control social media and news reporting. This
problem is an ongoing challenge for this study and others conducted in China and other
countries with centralized or authoritarian regimes.
This manuscript makes several contributions to research and public policy practice. Through
research on the network governance model, readers can understand how network governance
operates under the centralized system in public health emergencies. The performance of the
two provincial governments in the main stages of emergency management is discussed in
detail.
This study compares core government leaders’ backgrounds and attitudes, path dependence,
the role of mass media in public health crises, the implementation of epidemic prevention
policies in the two provinces, and the effectiveness of post-disaster recovery to explore
vigorous government activities within a centralized system. From the perspective of policy
practice, this manuscript provides several suggestions for policymakers to consider during
public health emergencies, although implementing them in a context like China comes with
several essential cautions.
This manuscript puts forward the following implications. First, following scientific and
reasonable operating rules can lead to better outcomes. Following Provan and Kenis (2008),

trust, goal consensus, and competencies among network participants are critical to network
governance performance. On the one hand, increasing the emphasis on professionals and
empowering them to participate in decision-making during the preparation, response, and
recovery of the epidemic prevention network leads to better outcomes. Moderately reducing
decisive top-down intervention can increase the independent participation of various
stakeholders. Leaders can mobilize social organizations and individuals while maintaining the
government’s dominant position in public affairs to realize excellent administrative
performance and shared value.
Second, although this is a daunting task for the Chinese context, I suggest releasing the
media, opening up information interaction, and allowing the normal flow of information are
essential for network governance. By enhancing openness before emergencies turn into large-
scale disasters, citizens can protect themselves more effectively.
Third, various authors have noted the difficulty of intervening in path-dependent processes
(Fortwengel, 2020). In short, path-dependent processes create a tacit acceptance from the
people who are embedded in them; these individuals are generally unaware of these
processes' influence on them. Chinese contexts may be particularly challenging because most
institutionalized practices are captured in top-down directives and rules. Thus, changing or
intervening in such processes is complicated by the reluctance of individuals to deviate from
instructions. I have no simple suggestions for changing these systems. Still, recent
developments in the literature (Hanger-Kopp et al., 2021) may be helpful to Chinese planners

in introducing systems that encourage leveraged change in existing path-dependent systems.
This approach requires that high-level leaders give their blessing to such innovations.
COVID-19 is still spreading worldwide and may affect humans for a long time. Establishing
and improving a mechanism to ensure people’s life safety and long-term economic benefits
requires innovation in medical technology and officials and decision-makers strengthening
the formulation and implementation of public epidemic prevention policies. By comparing
the emergency management networks of two Chinese provinces in response to the epidemic,
this
manuscript can draw valuable experiences and lessons.
CHAPTER 2 POLICY IMPLEMENTATION IN CHINESE LOCAL
GOVERNMENT
2.1 Chapter Overview
Incorporating insights from implementation theory and emergency management, this
manuscript examines the performance of the Henan and Shanghai provincial/municipal
governments during their early response to COVID-19 in 2020. The study reveals that the
Chinese approach to COVID-19 policy implementation diverges from traditional models
found in the existing literature. While it mirrors some of these conventional models, it also
showcases distinctive Chinese attributes. Furthermore, the paper posits that during the
COVID-19 response, Henan's strategies were predominantly steered by provincial
governments, with grassroots organizations playing a pivotal role. In stark contrast,

Shanghai's pandemic response strategy was primarily orchestrated by government
departments, with a significant reliance on professional bureaucrats for guidance and
execution.
Keywords: COVID-19, policy implementation, provincial government, Chinese
characteristics, comparative studies
2.2 Introduction
Moulton and Sandfort (2017) defined implementation as deliberate, institutionally sanctioned
change to a public service intervention legitimated partly by political authority. As Teets
argued (2016), it is one of the most successful paths to permit governors to respond to local
problems. I suggest that the importance of policy implementation can be summarized as
follows: In addressing urgent and intricate public matters, effective policy implementation
can result in more adept and resourceful solutions, benefiting citizens, organizations, and
broader societies. Furthermore, thorough policy implementation can optimize the capabilities
of organizations and individuals, promoting continuous improvement, elevating the caliber of
public programs, and fostering sustainable growth. Additionally, robust policy
implementation promotes open information exchange, fostering a culture of mutual learning
and knowledge dissemination among policymakers, stakeholders, and the general populace.
This boosts public trust and engagement, engendering a collective sense of responsibility and
ownership.

In late January 2020, due to the failure of the Hubei provincial government to control the
epidemic effectively, COVID-19 was directly out of control. It became a significant public
health emergency in China (“Wuhan Pneumonia”, 2020). One after another, provincial
governments implemented emergency management policies to respond to this unprecedented
virus according to internal and external conditions. This manuscript raises the following
research questions: RQ1a: Did the Chinese response to COVID-19 adhere to existing policy
implementation forms as depicted in the extant literature? RQ1b: If not, how did the form of
policy implementation differ for the Chinese context? RQ2: How did the response differ
between Henan Province, an internal province, and Shanghai Municipality, a directly
administered municipality with a substantial international environment, and what are the
implications for a Chinese characteristics model of policy implementation? I intentionally
invoke a comparison between those who emphasize differences in governmental and societal
systems as the result of different cultures (e.g., Hofstede, 2001; House et al., 2004) and others
who argue for the importance of different emergent institutional systems (e.g., North, 1991;
North, Wallis & Weingast, 2009; Acemoglu & Robinson, 2012). I suspect the differences in
policy implementation in China are primarily because of institutional differences, including a
centralized system and top-down governance mechanisms.
Based on the characteristics of an authoritarian government’s unique administrative model,
this manuscript explores how Henan and Shanghai performed their respective functions,
mobilized public resources, and cooperated with external organizations. Thus, my
comparative cases examine how public and private hospitals, social media, private

enterprises, and universities responded to this public health crisis, safeguarded public interest,
and reduced economic losses. These comparative cases provide valuable information for
emergency managers and
researchers to look for differences in response to the outbreak.
2.3 Literature Review and Background of COVID Response in Henan and Shanghai
2.3.1 Literature Review: Forms of policy implementation
Policy implementation involves seeing the policy through by ensuring sufficient resource
provision, competent management and control structures, and appropriate bureaucratic rules
and regulations (Wolman, 1981). Mazmanian and Sabatier (1983, 21) maintained that the
degree of success in implementing a policy is determined by three "broad categories" of
variables: “(1) the tractability of the problems being addressed, (2) the ability of the
[legislative] statute [establishing the policy] to structure favorably the implementation process
and (3) the net effect of a variety of political variables on the balance of support for statutory
objectives.”
Van Meter and Van Horn (1975 and 1976) offered a framework for understanding the
relationship between acceptance and use through categorizing the obstacles to the successful
implementation of public policy. Deriving from Kaufman’s (1973) analysis of the reasons for
noncompliance in public sector organizations, Van Meter and Van Horn (1976, 47) identified
three Fundamental barriers to policy implementation: dispositional problems (when

implementors do not want to do what they are supposed to do), communication problems
(when implementors do not know what they are supposed to do), and capability problems
(when implementors are not able to do what they are supposed to do)5. Viewed From this
theoretical perspective, accepting an expert system means that dispositional problems have
been overcome. Still, acceptance does not imply usage because implementation also requires
effective communication and sufficient resources to conquer capability problems.
2.3.1.1 Communication factors
Van Meter and Van Horn (1976, 466) contend that successful policy implementation requires
clear policy objectives and accurate and consistent communication among them so that
implementors know what is expected of them. A crucial part of communication is explicit
topmanagement support; studies of policy implementation (e.g., Ginsberg, 1981; Hage and
Dewar,
1973; Mohr, 1969; Zaltman and Duncan, 1977) have found that such explicit support is a
significant factor in successful policy implementation. Lucas (1976, 20) explained that
“management commitment is needed since management provides leadership and rewards to
members of the organization.” For policymakers, they need to set up clear goals to fulfill.
These goals fall into two categories: political goals, such as re-election, reappointment,
5 Edwards (1980) develops a very similar implementation framework, which includes
communication, resources, dispositions (or attitudes), as well as a fourth factor: bureaucratic
structure.

maintenance of power, and appearing legitimate, and policy goals, such as adopting beneficial
policies and attracting large tax bases to underwrite government activities (Gilardi, 2010).
2.3.1.2 Dispositional factors
As for attitudes—or "disposition"—of implementors toward the policy being implemented,
Van Meter and Van Horn (1975, 482) assert that "implementation may fail because
implementors refuse to do what they are supposed to do. Dispositional conflicts occur
because subordinates reject the goals of their superiors for numerous reasons: they offend
implementors' values or extra-organizational loyalties; they violate implementors’ sense of
self-interest; or they alter features of the organization and its procedures that implementors
desire to maintain."
Berry (1997) developed a theory about the attitudinal factors that lead an employee to accept
an expert system. It included factors that relate to what Kaufman (1973, 3) called the
employee's "sense of self-interest," as well as other factors that relate to the system's
usefulness to the broader organization. Regarding self-interest, the theory asserts that
managers face competing priorities concerning expert systems. As Mintzberg (1973, 15)
argued, managers prefer structured, routine decisions over complex, unstructured ones.
Hadden (1986, 587) concluded that expert systems "can extend the scope of tasks that are
partly structured by embodying that part of the underlying knowledge that can be
systematized." Thus, the preference for structured, routine decisions should promote
managers' acceptance of an expert system. At the same time, since expert systems structure
decisions to the point of identifying a "preferred" alternative, expert systems might be seen as

a threat to a manager's discretion (Coursey and Shangraw, 1989; Hauser and Hebert, 1992).
Thus, to the extent managers desire to protect their discretion, they might resist relying on an
expert system.6
2.3.1.3 Capability factors
By capability problems, Van Meter and Van Horn (1975; 1976) refer to various resource
limitations. To overcome these problems, implementing staff must be adequately prepared.
Specifically, preparation should be enhanced by a sufficient educational background and
specific training in implementing technology. Highly educated staff are likely to be able to
adapt more quickly to the intellectual demands posed by the utilization of computer
technology (Fuerst and Cheney, 1982). However, a solid educational background is no
substitute for good training with the specific software. Edwards and Sharkansky (1978) found
that adequately training staff was one of the two most critical steps top management can take
to ensure effective policy implementation (Zaltman and Duncan, 1977). Likewise, the
technology implementation
literature links training to agency achievement of computer benefits (Fuerst and Cheney,
1982; King and Kraemer, 1985; Lucas, 1974). Also, more professionalized policymakers can
6 While the Supervisor Assistance System is a consultative system that can be overridden by
managers if they disagree with its advice, the department's policy is that managers must
provide a detailed justification in their disciplinary recommendation if they override the
system's recommendation.

produce more effective policy outcomes than others who are “less professional” (Shipan et
al., 2006).
2.3.2 Background: Chinese Context
Central–local relations are critical to developmentalism because they highlight an intriguing
puzzle in public administration, especially in large states: how policies decided at higher
echelons of the formal system can be implemented by the multitude of intermediary and local
actors across the system.7 In the case of China, an additional dimension has been the contrast
between the authoritarian façade of the Chinese regime—which suggests a higher propensity
for central control—and conspicuous implementation gaps over many policy arenas (Li, L.
C., 2010). Within the framework of state-society relations, China adopts a centralized
“statecentered top-down approach” (Sellers, 2011). Some observers describe the government
of
China as an authoritarian political system under the political leadership of the Chinese
Communist Party (hereafter: CCP) (Minzner, 2011; Wang, 2015). Following Minzner (2011)
and Wang (2015), Chinese provincial governments are under the jurisdiction of the central
government, and, in turn, they supervise the municipal governments within their jurisdictions.
7 The notion of ‘central–local relations’ as used in this article follows the convention of the
China studies and central–local relations literature to refer to the relationship between the
national and provincial (regional) levels of government, whilst acknowledging the plurality of
government tiers beyond the central level in China (Goodman, 1999, 2002).

Because of their robust governance mode, all levels of government are dominant in public
resource mobilization and organizational capacity. Thus, local officials manage social affairs
through top-down policies. This is especially evident in the face of large-scale disasters, for
which governmental leaders claim advantages of “nationwide systems.”
Similarly, policy implementation could occur in non-democratic or centralized countries if the
national governments have delegated certain economic or administrative powers to the
subnational governments (Zhang and Zhu, 2014). In general, the central government sets the
goals and policy agenda, leaving the details of policymaking to provincial and municipal
governments (Tai et al., 2022). Once they obey the broad central government goals,
subnational governments may interpret primary directives, enact new policies, or selectively
implement policies that reflect foremost priorities and local conditions, capacities, or
priorities (Tai et al., 2022). The subnational governments have delegated various economic
and administrative powers, and most local governments can implement new policy practices
(Cai and Treisman 2009; Bardhan 2002; Treisman 2000). The power of the local governments
derives from the central government, although major decision‐making is retained by the
central government (Jin, 1999). However, the provincial government’s policy implementation
could also increase policy influence by obtaining the central government’s approval (Deng et
al., 2018).
Since establishing the People's Republic of China, the CCP has maintained strict personnel
control of the subnational governments. China’s political leaders are not elected by citizens
within their jurisdictions. Instead, they are selected and appointed by superior committees of

the CCP based on economic performance, social stability, or political factions (Choi 2012;
Shih 2008; Shih, Adolph, & Liu 2012). The central government has full authority to
determine the political careers of subnational leaders, including evaluation, monitoring,
appointment, promotion, rotation, and demotion (Choi 2012; Edin 2003). All subnational
governments may implement the policies in localized ways, but they are still constrained by
the more extensive system, where the central government can directly interfere on an ad hoc
basis (Heilmann, 2008; Schubert & Alpermann, 2019). Under Xi Jinping’s era, loyalty is
particularly critical to cadre promotion (Teets et al., 2017). Those who do not want to be
demoted must maintain a minimum level of competency but also need the approval and
support of their superiors to advance (Li & Gore, 2018). Also, while governance in China can
be seen as a series of fluctuations between centralization and decentralization, Xi’s era is
primarily characterized by “top-level design,” which means more specific directives from
Beijing with more precise control over the implementation process (Schubert & Alpermann,
2019). Therefore, local governments must pay serious attention to the central government’s
policy signals.
2.3.3 Historical Precedence for Responding to Public Health Emergencies in China
China experienced the impact of SARS in 2003. To deal with the virus effectively, China
passed the Regulations on Emergency Response to Public Health Emergencies on May 7,
2003, which was officially implemented two days later. After SARS was effectively
controlled, on August

28, 2004, the Law on the Prevention and Control of Infectious Diseases, passed on February
21, 1989, and implemented on September 1 of the same year, was revised again. At the same
time, the Emergency Response Law was passed on August 30, 2007, and implemented on
November 1 of the same year. In 2009, the H1N1 influenza pandemic caused 120,498
confirmed cases and 648 deaths in China (Tang, 2010). Since then, China revised the
Regulations on Public Health Emergencies on January 8, 2011, and the Law on the
Prevention and Control of Infectious Diseases on June 29, 2013, to improve the level of
response to public health emergencies. These policies suggest that, guided by relevant laws
and regulations, the Chinese government has continuously strengthened the governance of the
epidemic prevention network to improve its management capabilities in early warning,
decision-making, resource allocation, treatment implementation, and post-pandemic recovery.
Article 3 of the Law on the Prevention and Control of Infectious Diseases classifies infectious
diseases into Types I, II, and III. Type I refers to plague and cholera. Type II includes
infectious atypical pneumonia, AIDS, viral hepatitis, avian influenza, etc. Type III has
influenza, mumps, rubella, etc. Article 4 of this law stipulates that among the Type II
infectious diseases, SARS, pulmonary anthrax, and highly pathogenic avian influenza,
prevention and control measures for Type I contagious diseases should be taken. For sudden
infectious diseases of unknown cause, where prevention and control measures for Type I
infectious diseases as referred to in this Law need to be taken, the health administrative
department of the State Council shall promptly report to the State Council for approval and
announce and implement the relevant prevention and control measures.

As early as January 19, 2020, the Chinese Health Commission confirmed the human-to-
human transmission characteristics of COVID-19 as observed in Hubei Province (State
Council
Information Office in China, 2020). With the approval of the State Council, the National
Health
Commission listed it as a Type II infectious disease. The prevention and control measures
required treating it for Type I contagious diseases. At 10 a.m. on January 23, 2020, Hubei
Province announced the implementation of a city-wide closure policy in response to the
outof-control epidemic (Wang, 2020). With the outbreak's spread in Hubei, governments at all
levels became aware of effective measures and their shortcomings in the preparedness and
response phases for COVID.
Articles 39 to 49 of the “Law on Prevention and Control of Infectious Diseases” are measures
related to epidemic control, mainly aimed at epidemics that have emerged and spread on a
large scale. The law pointed out that medical institutions should promptly carry out medical
observation measures for suspected and confirmed cases of Type I infectious diseases and
take necessary treatment and transmission control measures for patients with Type II and III
infectious diseases as needed. In terms of epidemic notification, following legal guidelines,
disease prevention and control institutions should promptly report critical information,
including time, location, control plan, and sanitation progress, to higher-level units. During
the large-scale spread of the epidemic, governments at all levels above the county should
fully mobilize public resources such as human resources and property to control the source of
infection, cut off the transmission route, and protect the susceptible population. These include

suspending work, business, and school, restricting or ceasing crowd-gathering activities, and
controlling and culling infected animals. In addition, the State Council holds extensive
authority to orchestrate nationwide mobilization of personnel and resources, and to
commandeer housing, transportation, and various facilities and equipment as deemed
necessary, enabling a centralized response to national exigencies and strategic initiatives.
2.4 Methods
This study conducts a comparative case analysis (Hamel, 1993; Merriam, 1988; Stake, 1995;
Yin, 2018) between Henan Province and Shanghai Municipality in their COVID-19
responses. Also, this study uses cross-case analysis to group common responses to interviews
and analyze different perspectives on central issues (Patton, 1990). I focus on interpreting
why Henan and Shanghai implemented other preparedness, response, and recovery strategies
through information mining and coding toward multiple data sources, including media
reports, government archives, and datasets summarized by the Health Commissions of these
two provinces. These three phases derive from the U.S. Integrated Emergency Management
System
(IEMS) created by FEMA leaders (Federal Emergency Management Agency, 2010; Giuffrida,
1985).8 I identify the foremost provincial leaders, specialized bureaucrats, social
organizations,

8 Some observers note that China’s emergency management activities do not map neatly
against the four phases as characterized by FEMA and other Western country models
(personal communication, Robert McDaniel, March 19, 2023). I impose them on the findings
in this study because they provide a useful analogy for relating these activities to Western
audiences. A Chinese proverb suggests that it may at times be possible to grasp both the
eyebrow and the beard; this metaphor is useful for understanding that in China, as elsewhere,
emergency or disaster activities may simultaneously be directed to response, recovery, and
preparedness, particularly when leaders don’t know in advance the best sequencing of
activities. This is clearly the case in the Chinese approach to COVID.
and individuals and their roles and impact in performing the COVID-19 response. This study
also highlights the critical events concerning different strategies the two provinces took under
the same political system.
There are two reasons why this manuscript chooses Henan Province and Shanghai
Municipality. First, the two regions are generally considered to have achieved remarkable
results in responding to the epidemic; thus, examining where their policy responses originated
is helpful. In addition, Henan Province is an inland province in China, while Shanghai City is
a coastal province and the first region in China to open to the world. Differences in
geographical location and styles of governance could lead to implementing different policies
in these two provinces.
The study sampled archival materials for information mining and analysis by delineating time
ranges and specific keywords. The time range extended from January 21, 2020, when Henan
Province started their preparation work toward COVID-19, to March 19, 2021, when

statistics bureaus of both Henan Province and Shanghai Municipality turned in their annual
economic summaries.
I developed an iterative approach to identifying keywords in my search for relevant archival
documents and media reports. My initial search terms were Henan, Shanghai, pandemic, and
2020. I eliminated materials that were primarily propagandistic, such as materials that were
self-aggrandizing or excessively praising higher levels of government. To identify more
detailed information, I added essential keyword terms found in initial documents and worked
iteratively between the keyword list and subsequent documents. This search approached
saturation when the following documents I found contained no additional new terms or
information.
While interviews may have been helpful, the time and economic cost of travel to and from
China for empirical research is too great, and lockdowns would constrict the author’s
movements. On the other hand, if interviews were conducted online or through email,
interviewees’ candor may be limited for fear of government monitoring. I used primarily
archival materials in the absence of interview data. I deliberately sought materials from BBC,
the New York Times (NYT), Reuters, and the World Health Organization (WHO) to check
against the accuracy of Chinese government information.
This study uses qualitative methods to study policy implementation, for which Starke (2013)
has recommended three approaches. The first of these methods is cross-case analysis, which
systematically investigates qualitative similarities and differences of values on theoretically
relevant variables across several cases. The second is process tracing. This is understood as an

attempt to “identify the intervening causal process—the causal chain and causal mechanism
— between an independent variable (or variables) and the outcome of the dependent
variable” (George and Bennett 2005, 206). The third is counterfactual reasoning. In analyzing
the effectiveness of policy implementation by provincial or municipal governments, Levy
(2008) suggests that the clarity of the antecedents and consequents, the feasibility of the
antecedents, and the likelihood of observing the consequents when the antecedents occur, are
crucial. These factors collectively contribute to a comprehensive understanding of how
policies are enacted and their impacts measured.
2.5 Findings
Henan and Shanghai reflected the strong government’s consistent style of resource allocation
in response to COVID-19. From pre-disaster preparation and disaster response to post-
disaster recovery, officials reflected the top-down management and control mode. Both the
Governor of Henan Province and the Mayor of Shanghai were informed that epidemic
prevention in Hubei Province was out of control and received the State Council’s request for
epidemic prevention work. Under such circumstances, Henan and Shanghai completed the
epidemic prevention and preparation work in time to avoid the COVID-19 outcomes that
Hubei Province experienced.
Table 2.1 and 2.2 show that Henan and Shanghai adopted different measures to control the
epidemic. Although there were differences in the time required to end the first-level public
health response, Henan and Shanghai generally responded effectively to the epidemic (Yang,
2020; Gao, 2021). From the perspective of the number of confirmed cases, as of March 31,
2020, the cumulative number of confirmed cases in Henan Province, with a population of
99.37 million (2020), was 1,273 (Henan Province Bureau of Statistics, 2021a; Henan
Provincial Government Net, 2020). For Shanghai, with a population of 24.87 million (2020),
the number was 354 (Shanghai Bureau of Statistics, 2020b; Dong, 2020). At the end of March
2020, the number of deaths in Henan was 22 (Henan Provincial Government Net, 2020), and
in Shanghai, six individuals died from COVID-19 (Shanghai Municipal Health Commission,
2020c). These numbers for Henan and Shanghai were a fraction of the 68,481 cumulative
cases and 3301 deaths in Hubei Province during the same period (Health Commission in
Hubei Province, 2020).
Table 2.1 Key Economic Indicators in Henan and Shanghai Affected by COVID-19 in
the 1st Quarter of 2020 (Henan Province Bureau of Statistics, 2020) (Shanghai Bureau of
Statistics, 2020a)
Henan Shanghai
GDP CNY 1151.015
Billion
CNY 785.662
Billion
Growth Rate -6.70% -6.70%
The added value of the primary industry CNY 68.871 Billion CNY 1.530 Billion
Growth Rate -9.70% -18.20%
The added value of the secondary industry CNY
Billion
474.569 CNY
Billion
174.523
Growth Rate -8.10% -18.10%
The added value of the tertiary industry CNY
Billion
607.575 CNY
Billion
609.609
Growth Rate -4.90% -2.70%
The growth rate of industries above the -6.80% -17.40%
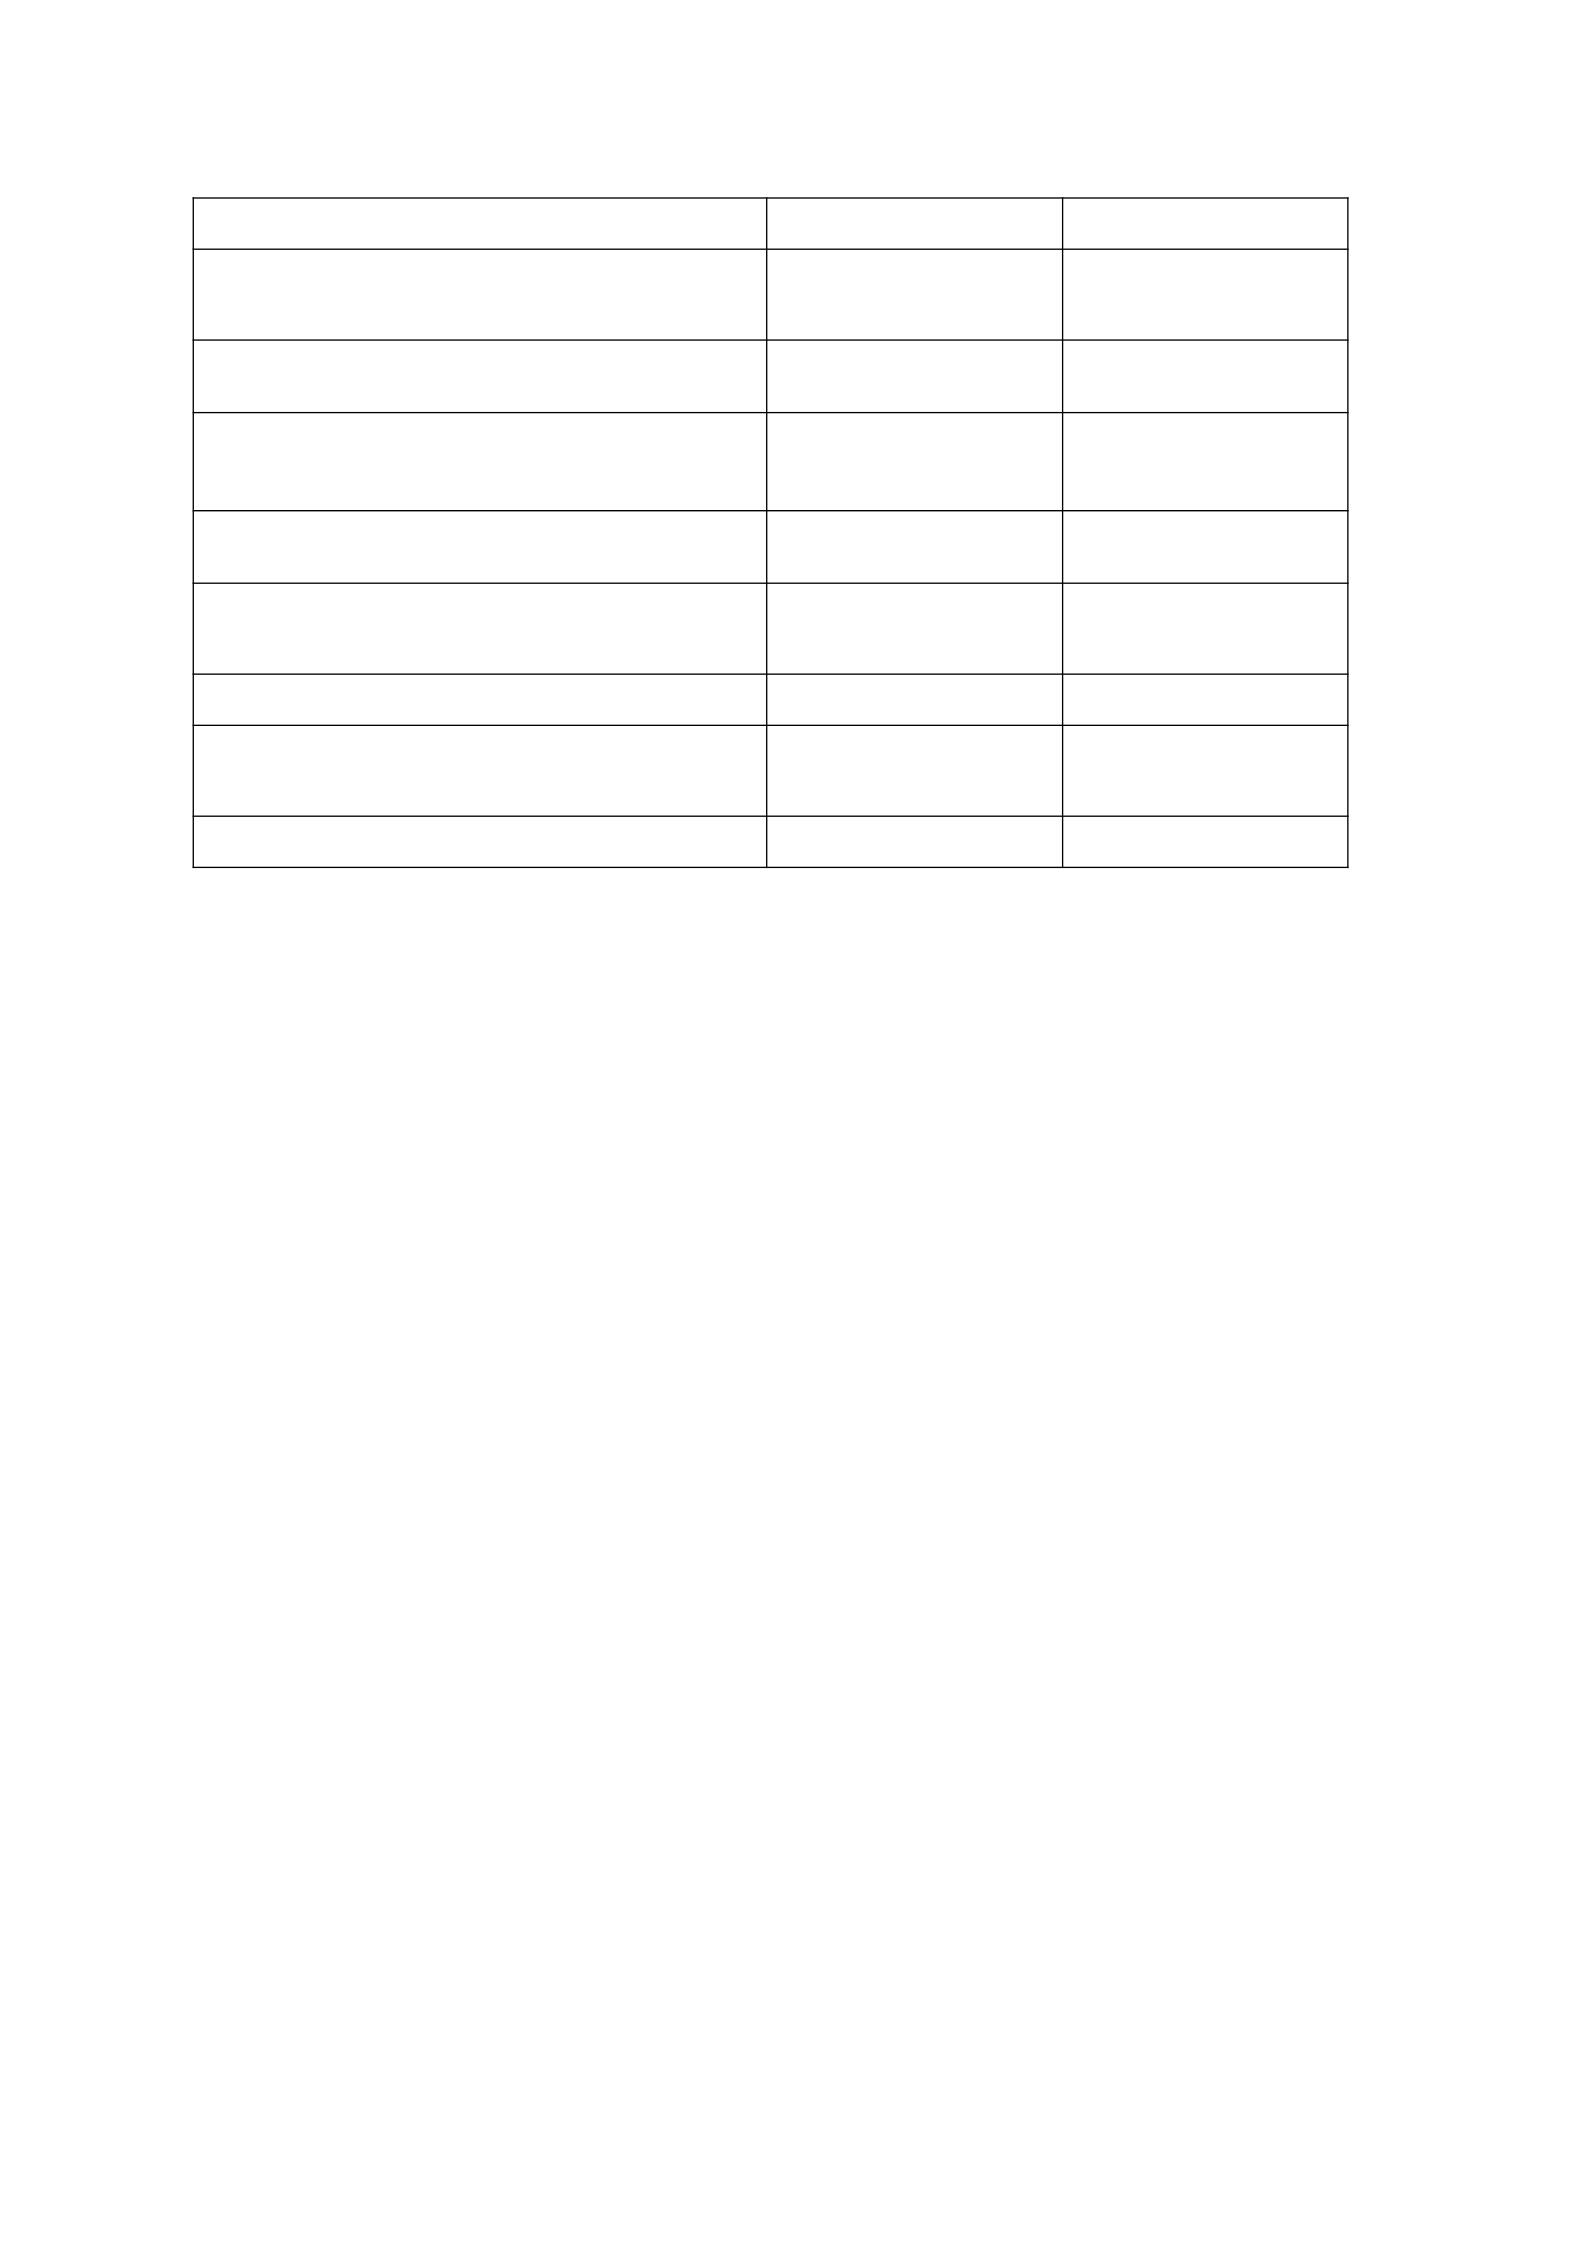
designated size
The growth rate of investment in fixed
assets
-7.50% -9.30%
Real estate growth -2.30% -10.30%
The total retail sales of social consumer
goods
CNY
Billion
454.671 CNY
Billion
306.034
Growth Rate -21.90% -20.40%
Per capita disposable income of urban
permanent residents
CNY 9088.18 CNY 20646
Growth Rate 0.80% 4.90%
Per capita disposable income of rural
permanent residents
CNY 3939.88 CNY 10726
Growth Rate 4.30% 4.40%
Figure 2.1 illustrates the trajectory of the cumulative number of COVID-19 confirmed cases
in
Henan Province up to March 31, 2020. It reveals a notable trend observed in both Henan and
Shanghai concerning the evolution of confirmed cases over time. Starting from mid-February,
both regions initiated a first-level response to the public health emergency, implementing
stringent control measures. These actions had a pronounced impact on the epidemic's course
in both locales. The daily increment of new cases experienced a sharp decline, steadily
dwindling to nearly zero as these measures took effect. This downturn in case numbers
reflects the efficacy of the rapid and comprehensive control strategies deployed, underscoring
the importance of decisive action in the face of public health crises.
Following mid-March, a specific policy adjustment in Shanghai further influenced the
reported data on confirmed cases. The city made the decision to exclude imported cases from
its cumulative count, a move detailed in the research by Dong (2020). As a result, Shanghai's
cumulative confirmed case count stabilized at 354, no longer reflecting new cases originating

from outside its borders. This policy adjustment marks a significant point in Shanghai's
management of the pandemic, illustrating a shift in focus towards controlling the spread of
the virus from international sources. The approaches of Henan and Shanghai, as detailed in
the figure, provide insight into the dynamic and evolving strategies employed to navigate the
challenges posed by the COVID-19 pandemic.
2.5.1 Henan Province
2.5.1.1 Preparedness
Following the detection of COVID-19's first case in Henan Province on January 21, the local
government swiftly enacted a comprehensive series of strategic measures aimed at curbing
the virus's spread. A significant focus was placed on protecting vulnerable groups within the
community. Extensive protective actions were implemented across 3,314 nursing homes and
79 child welfare institutions, emphasizing the safety and health of the populations therein.
Rigorous infection control protocols, regular health screenings, and stringent sanitation
practices were established. As a result of these meticulous efforts and rigorous preventive
protocols, there were zero reported COVID-19 cases among the 125,000 elderly residents and
over 4,600 children housed in these facilities. This remarkable outcome showcases the
effectiveness of the protective measures implemented, demonstrating how targeted actions
can significantly mitigate health risks in vulnerable populations during a global pandemic.
Table 2.2 Comparison of economic indicators between Henan Province and Shanghai in
2020 (Henan Province Bureau of Statistics, 2021a; Shanghai Bureau of Statistics, 2021)
Henan Shanghai
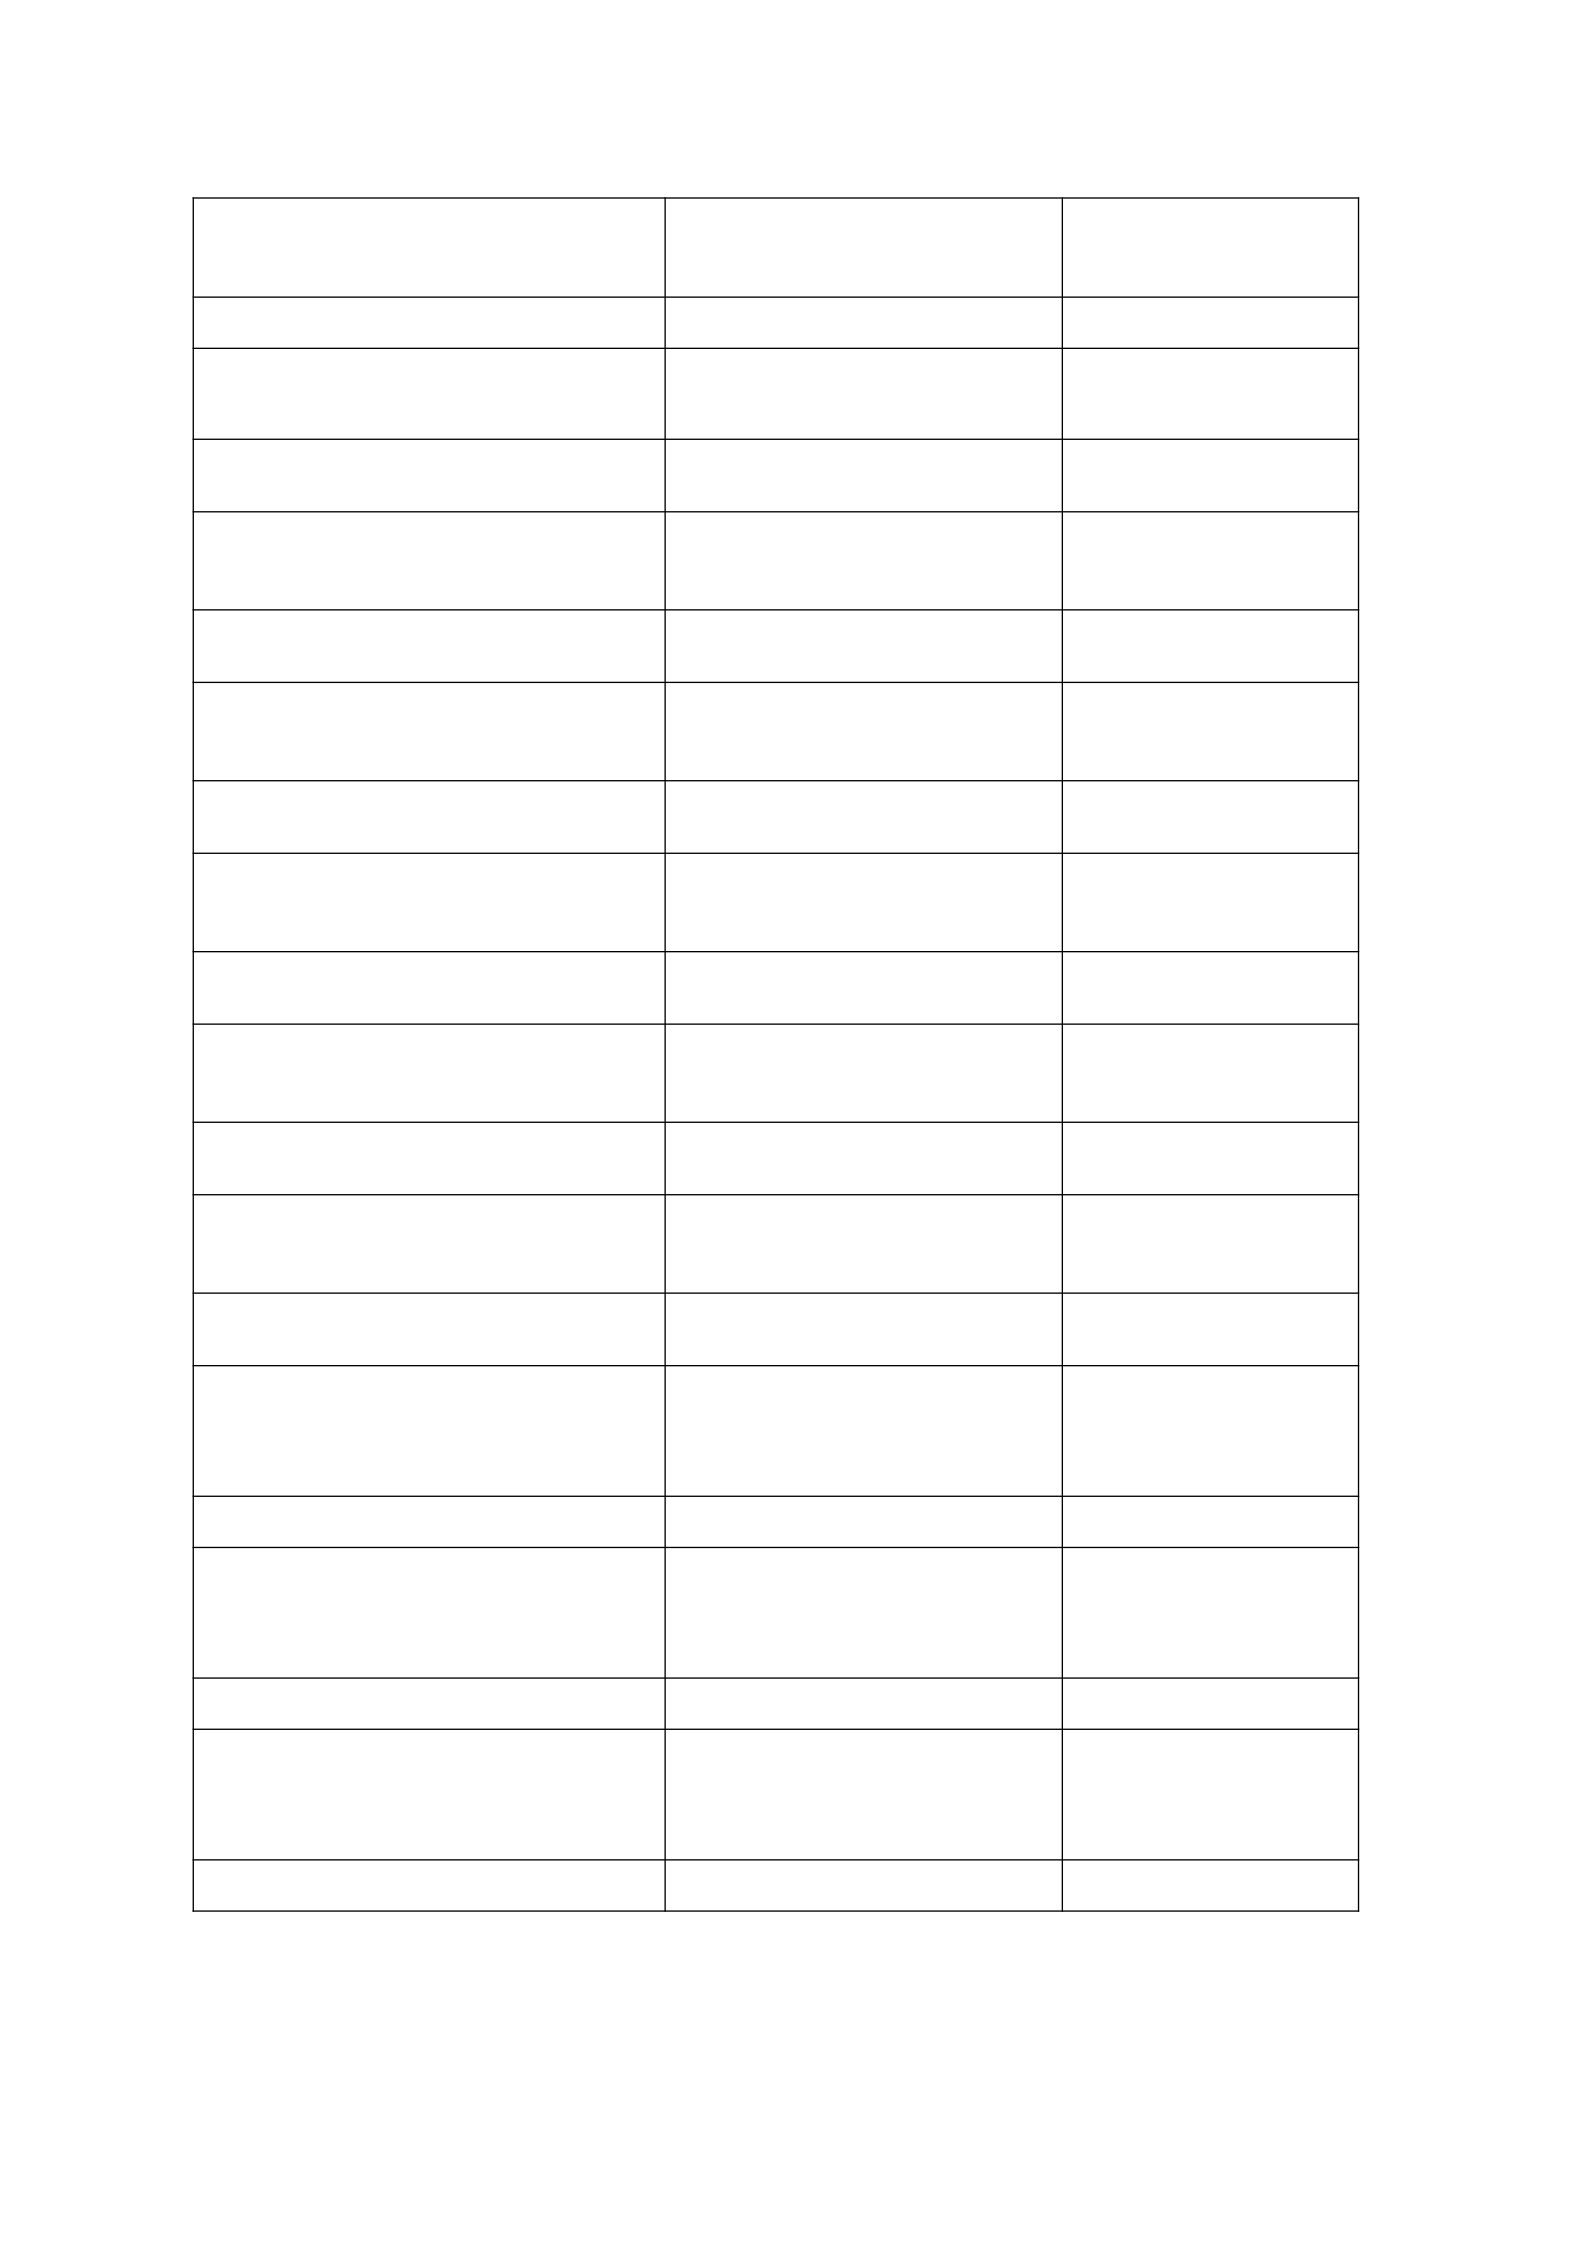
GDP CNY 5499.707 Billion CNY 3870.058
Billion
Growth Rate 1.30% 1.70%
The added value of the primary
industry
CNY 535.374 Billion CNY 10.357 Billion
Growth Rate 2.20% -8.20%
The added value of the secondary
industry
CNY 2287.535 Billion CNY
Billion
1028.947
Growth Rate 0.70% 1.30%
The added value of the tertiary
industry
CNY 2676.801 Billion CNY
Billion
2830.754
Growth Rate 1.60% 1.80%
The added value of the real estate CNY 778.229 Billion CNY
Billion
469.875
Growth rate 3.80% 11.00%
The total value of import and
export of goods
CNY 665.482 Billion CNY
Billion
8746.310
Growth rate 16.40% 3.80%
The total retail sales of social
consumer goods
CNY 250.277 Billion CNY
Billion
1593.250
Growth rate -4.10% 0.50%
Provincial/city per capita
disposable income of residents in
both province/municipality
CNY 24810.10 CNY 72232
Growth rate 3.80% 4.00%
Per capita disposable income of
urban permanent residents in both
province/municipality
CNY 34750.34 CNY 76437
Growth rate 1.60% 3.80%
Per capita disposable income of
rural permanent residents in both
province/municipality
CNY16107.93 CNY 34911
Growth rate 6.20% 5.20%
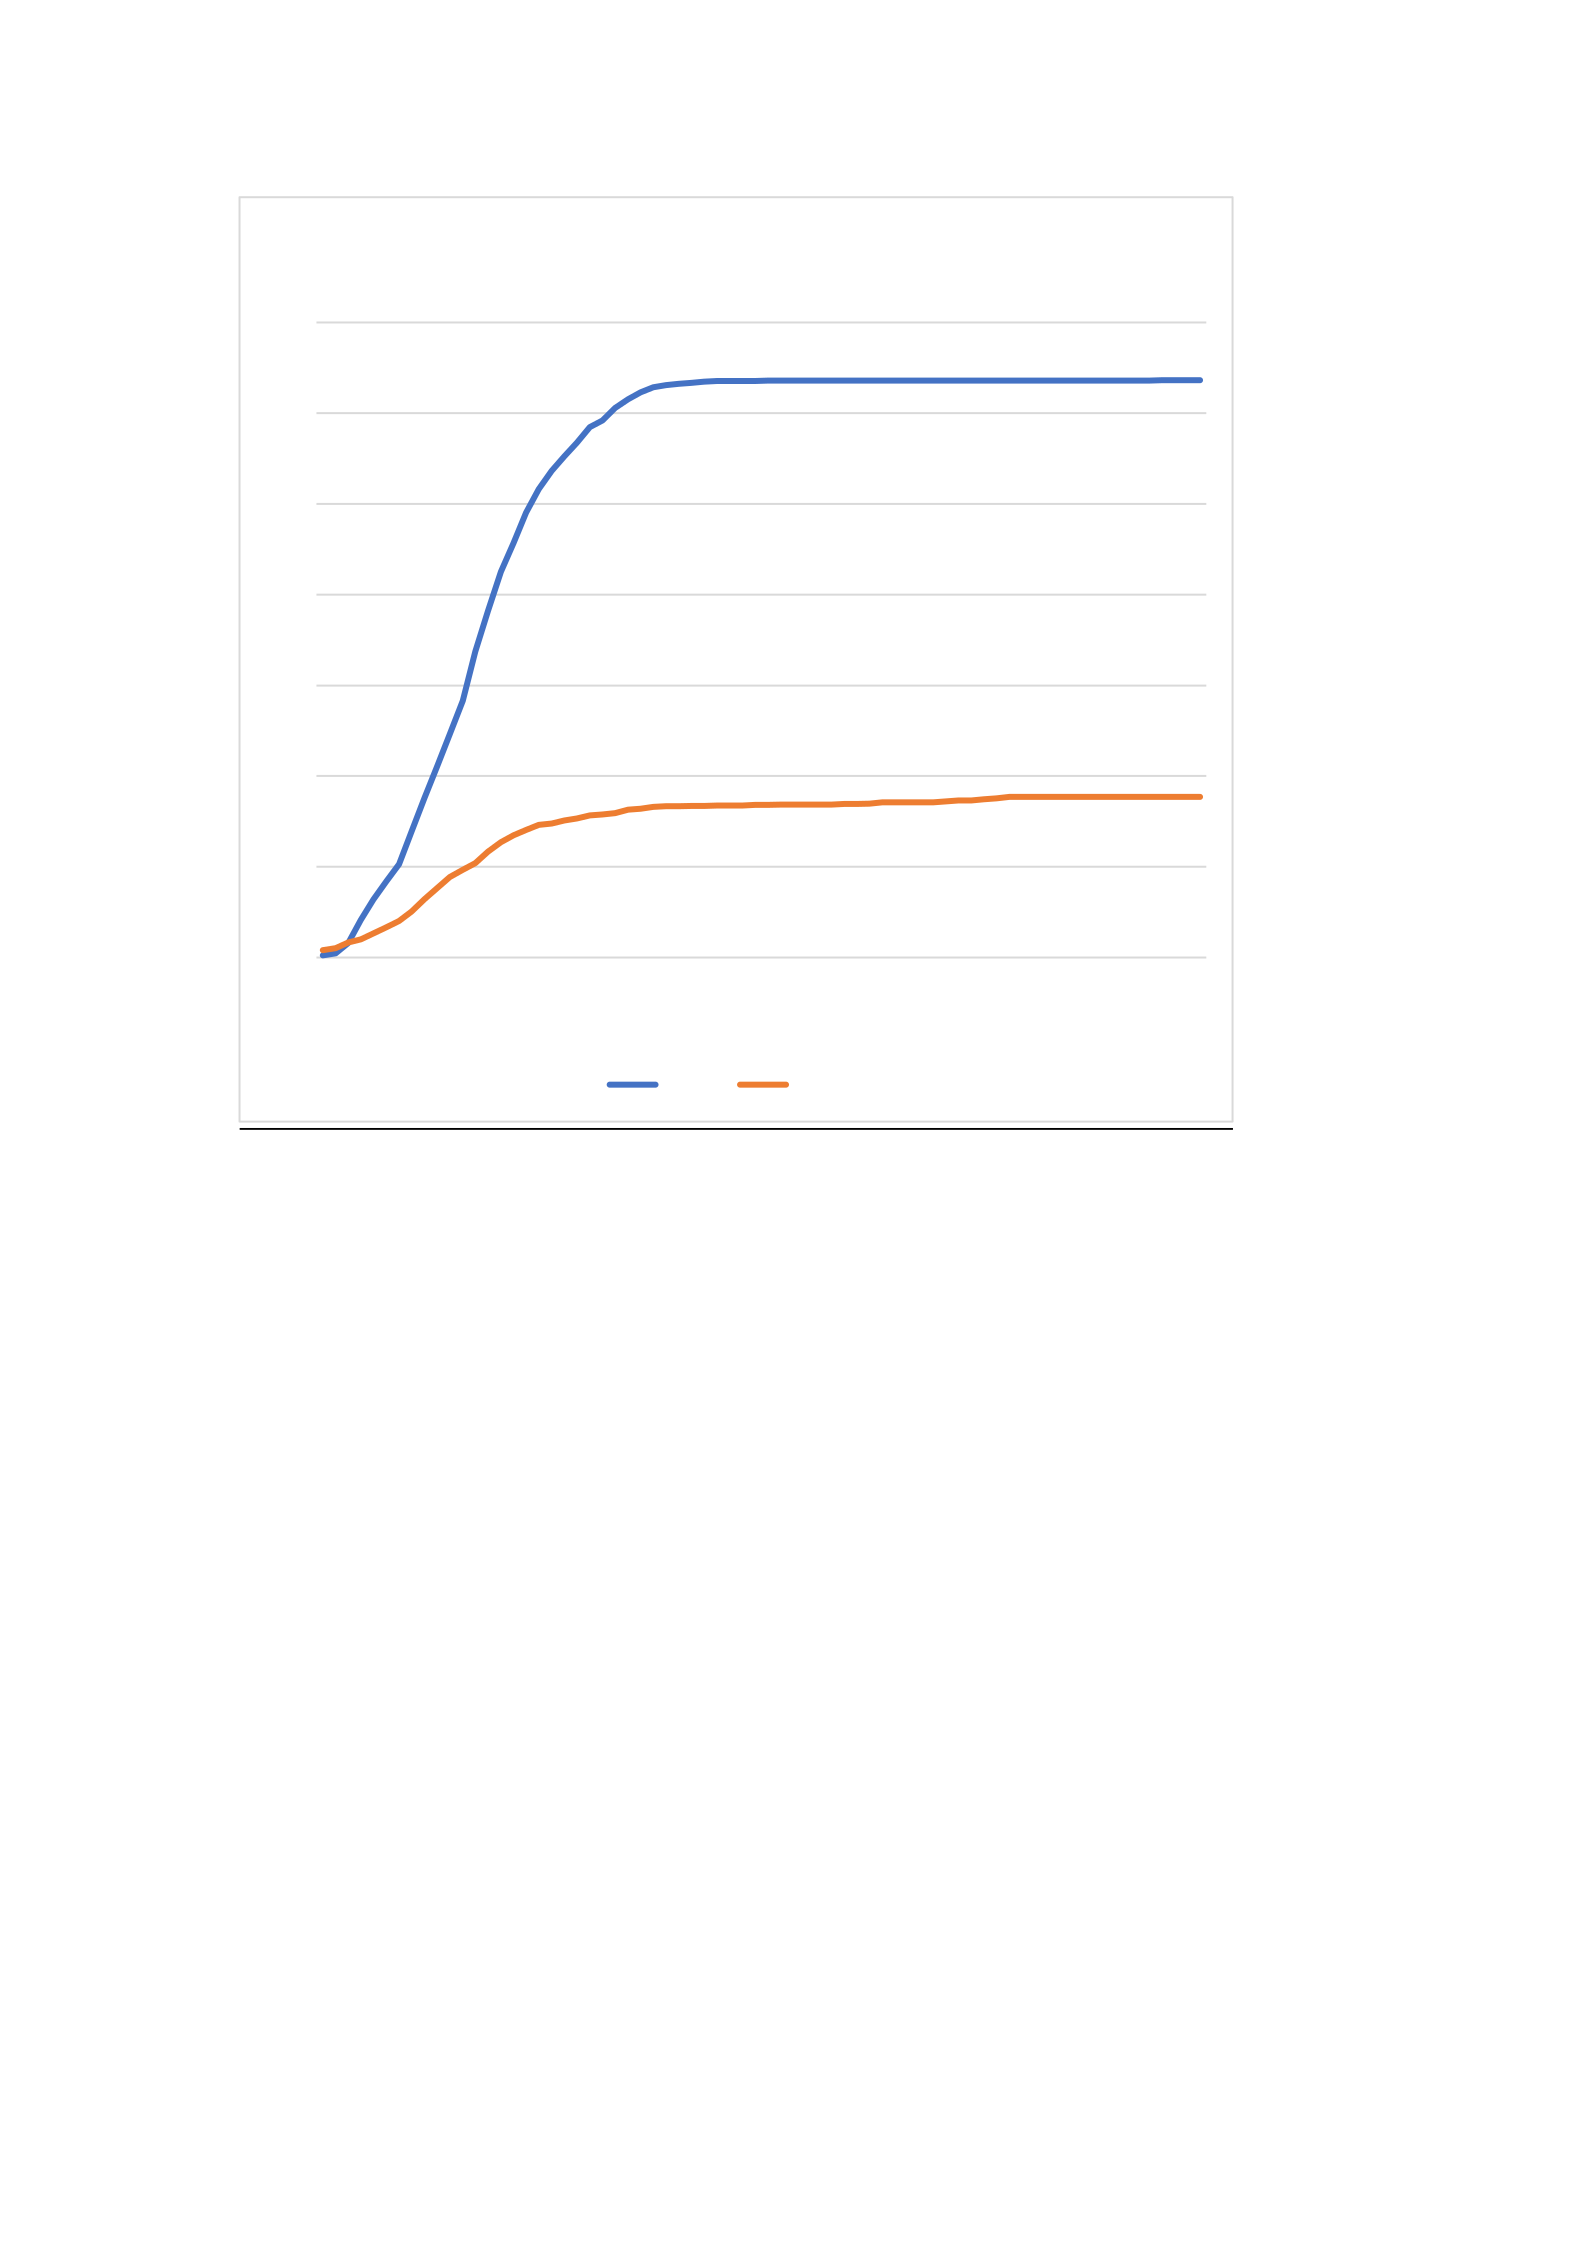
Figure 2.1: Comparative trends in cumulative confirmed cases of COVID-19 in Henan
and Shanghai in the first quarter of 2020 (Health Commission of Henan Province, 2020;
Shanghai Municipal Health Commission, 2020)
In tandem, efforts to control the virus's source were initiated, including a ban on the sale and
on-site slaughter of live poultry, alongside a mandate for daily reporting on the implemented
corrective actions. Additionally, to disrupt the virus's transmission, Henan identified 130
hospitals for dedicated COVID-19 treatment and established 525 fever clinics by January 23,
strategically reducing the disease's spread through healthcare and public transportation
systems. These targeted actions, grounded in protecting the most susceptible, controlling the
infection's origin, and cutting off transmission routes, highlight Henan's effective and
0
200
400
600
800
1000
1200
1400
Jan. 22
Jan. 24
Jan. 26
Jan. 28
Jan. 30
Feb. 1
Feb. 3
Feb. 5
Feb. 7
Feb. 9
Feb. 11
Feb. 13
Feb. 15
Feb. 17
Feb. 19
Feb. 21
Feb. 23
Feb. 25
Feb. 27
Feb. 29
Mar. 2
Mar. 4
Mar. 6
Mar. 8
Mar. 10
Mar. 12
Mar. 14
Mar. 16
Mar. 18
Mar. 20
Mar. 22
Mar. 24
Mar. 26
Mar. 28
Mar. 30
Changes in the cumulative number of confirmed cases in Henan
Province and Shanghai in 2020
Henan Shanghai

immediate response to the emerging health crisis, underscoring the province's commitment to
public health safety and pandemic management.
On the other hand, the public security bureaus of Henan Province launched 95 general
security checkpoints successively and established 6,318 joint public security checkpoints and
quarantine stations (Wang, 2020). On January 24, 2020, most scenic spots in Henan, such as
Shaolin Temple, announced their closure (Dengfeng Municipal People’s Government, 2020).
On January 25, 2020, the number of confirmed cases in Henan Province was 32 (Health
Commission of Henan Province, 2020). On the same day, Henan Province announced the
launch of a first-level response to major public health emergencies (Henan Provincial
People’s Government, 2020).
2.5.1.2 Response
In terms of centralized treatment of confirmed patients, Henan Province commissioned the
Provincial Maternal and Child Health Hospital to use information technology to build an
online free consultation platform for maternal and child health care in the province, officially
launched on January 31, 2020 (You, 2020a). Henan Province used new media and technology
such as online maternity schools, maternal and child health APPs, WeChat public accounts,
and microvideos. More than 300 provincial gynecology, obstetrics, and pediatrics experts
provided online services for key populations such as women and children concerning
disseminating information about epidemic prevention and control (You, 2020a). On February
12, 2020, Henan Province designated two provincial-level and 19 municipal-level hospitals

for treating pregnant women and announced this to the public to clarify priorities for
diagnosis and centralized treatment for vulnerable groups (You, 2020a).
For medical technology, Henan Province used a remote consultation system to allow
provincial experts to guide grassroots medical institutions' epidemic prevention work directly.
Henan Province dispatched 13 expert teams to 17 cities within its jurisdiction, with 39 experts
driving treatment, eliminating suspected cases, and improving treatment efficiency (Lei,
2020).
Henan Province COVID-19 Epidemic Prevention and Control Headquarters also issued a
notice to ensure the smooth passage of emergency supplies and personnel transport vehicles
for epidemic prevention and control. This notice required the provincial transportation
department to provide various emergency and living supplies for inter-provincial and
intraprovincial response to the epidemic. Local officials also implemented classification
management of Class A and B Pass8 for cargoes of critical production materials for medical
care (Fan, 2020).
As an urgent supply chain measure, the Henan Provincial Emergency Management
Department allocated 7,800 disaster relief tents and 3,000 folding beds for emergency support
8 Class A pass is applicable to the transportation of various emergency supplies, living
supplies, key production supplies, medical care and prevention and control personnel across
provinces to deal with the epidemic. Class B pass is applicable to the transportation of various
emergency materials, living materials, and key production materials in response to the
epidemic within the province.

for epidemic prevention and control (Song et al., 2020). On February 15, 2020, Henan
Provincial Drug
Administration issued the “Opinions on Promoting the Production Capacity Improvement of
Medical Masks and Medical Protective Clothing” to promote the improvement of supply
capacity and quality of epidemic prevention and control products (Henan Provincial Drug
Administration, 2020).
2.5.1.3 Recovery
Henan Province COVID-19 Epidemic Prevention and Control Headquarters issued the
“COVID-19 Prevention and Control Plan for Resumption of Work and Production of
Enterprises” (Henan Provincial COVID Prevention and Control Headquarters, 2020). This
plan guided various enterprises in preventing and controlling the epidemic scientifically and
resuming work and production orderly. The Department of Industry and Information
Technology of Henan Province released 132 cloud product services and application solutions
to help enterprises continue work and production (Liu, 2020). During the period from January
20 to February 12, banking institutions in Henan Province issued more than Chinese Yuan
(CNY) 10 billion in loans to key guarantee enterprises for epidemic prevention and control,
and the loan interest rate did not exceed the benchmark interest rate for the same loan period
(Zhao, 2020).
On March 10, 2020, the Henan Provincial Financial Supervision Bureau promulgated relevant
policies, putting forward 12 specific requirements for the leading financial institutions in the

province in terms of industry management, duty performance, policy services, and industry
supervision from the reduction to the cancellation of loan interest rates. This supported the
resumption of work and production of small, medium, and micro enterprises and accelerated
recovery (You, 2020b). The Department of Industry and Information Technology of Henan
Province also released 167 software products and system solutions for epidemic prevention
and control, encouraging enterprises to use information technology to help resume work and
production (Wang, 2020). On March 17, 2020, a significant development occurred in Henan
Province, China, amidst the ongoing efforts to combat the COVID-19 pandemic. The Henan
Provincial Big Data Administration, in collaboration with the Provincial Health Committee,
took a strategic step forward by officially issuing the “Henan Health QR Code” Management
Measures. The introduction of this QR code system represents a pivotal initiative in
leveraging technology to enhance public health measures and economic recovery. By
requiring individuals to present their health status through a simple scan of their QR code, the
authorities aimed to effectively monitor and manage the population's health, thereby
minimizing the risk of virus transmission while promoting a gradual return to normalcy (Gu,
2020).
2.5.2 Shanghai
2.5.2.1 Preparedness
On January 18, 2020, a suspected COVID-19 patient underwent surveillance and ongoing
testing in Shanghai (Ma et al., 2020). Two days later, Ying Yong, the Mayor of Shanghai,
required that all organizations and individuals strengthen the prevention and control of

suspected cases (Shanghai Municipal Health Commission, 2020a). The first confirmed case
appeared in Shanghai on January 20, 2020 (Shanghai Municipal Health Commission, 2020b).
On January 24, 2020, Shanghai announced the launch of a first-level response to major public
health emergencies, focusing on community-based prevention and control, group prevention
and control, and joint prevention and control to block domestic imported risks (Lin, 2020).
Regarding medical care, Shanghai concentrated resources from hospitals, medical staff, and
experts within its jurisdiction to screen local and hospitalized patients in Shanghai while
strengthening protection for medical staff (Shanghai Municipal People's Government, 2020a).
After the epidemic in Wuhan got out of control, the Shanghai municipal government imposed
a 14-day quarantine involving information registration, medical observation, housing, and
other restrictions on individuals entering from Hubei (Shanghai Municipal People's
Government, 2020a). After Shanghai launched the first-level response mechanism for major
public health emergencies on January 24, 2020, more than 4,200 tourist and cultural facilities
in the city were closed, 121 theaters were closed, 111 A-level scenic spots were closed, and
public places and sports venues were closed (Shanghai Municipal People's Government,
2020a). Shanghai used mobile phones, subways, buses, and large screens in buildings to
disseminate information that allowed the masses to protect themselves (Shanghai Municipal
People's Government, 2020a).
To protect the safety of susceptible groups, Shanghai shared scientific information for older
people through bulletin boards, windows, corridor publicity, family doctors, etc. (Shanghai
Municipal People's Government, 2020b). The wholesale volume of vegetables and meat in

major wholesale markets in Shanghai gradually increased, and most wholesale markets still
had dynamic reserves after daily transactions. By initiating communication with production
areas in other provinces, Shanghai effectively met the epidemic-driven consumption demands
of the public, ensuring a stable supply of essential goods and services during the crisis
(Shanghai Municipal People's Government, 2020b). This proactive approach helped maintain
public confidence and alleviate potential shortages.
2.5.2.2 Response
In the early stage of the outbreak, administrative screening of high-risk groups and isolation
management helped to stop the spread of the epidemic. Government media in Shanghai
released 4,570 Weibo and WeChat articles related to COVID-19 in January, covering
information disclosure, policy interpretation, epidemic prevention measures, and health
reminders in a timely and effective manner to enhance the public’s self-awareness of disease
prevention (Liang, 2020).
For medical treatment, in the early stage of the COVID-19 outbreak, Shanghai concentrated
on treating patients and designated two hospitals for treatment (Cao, 2020). Through the
formation of a multidisciplinary team, rescue strategies based on evidence-based medicine,
and novel treatment plans, the proportion of critically ill patients in Shanghai has continued to
decline, and the treatment model has shown results (Cao, 2020).
To minimize panic among public members seeking medical treatment, Shanghai reduced
crowd gathering and cross-infection in hospitals (Shanghai Municipal People’s Government,
2020d). The Shanghai Municipal Health Commission and Shenkang Hospital set up a "fever

consultation" platform. By organizing more than 60 physicians from 15 municipal hospitals,
this platform provided round-the-clock telephone consultation services for citizens in
respiratory, infectious diseases, and critical care medicine departments. Shanghai also
launched a WeChat mini-program called "Covid Studio" to provide online consultation
services (Shanghai Municipal People’s Government, 2020d).
In terms of transportation, Shanghai strengthened ties between map navigation companies
such as AutoNavi and Baidu and the municipal telecommunication department to provide
early warnings of passenger flow for the public and supervise vehicles entering Shanghai
(Shanghai Municipal People’s Government, 2020c). Shanghai increased public transportation
staffing and traffic lanes at major intersections to increase traffic capacity. Shanghai
recommended that citizens fill out epidemic prevention information online to minimize
investigation time at checkpoints, thereby improving traffic flow and ensuring smooth traffic
during the epidemic (Shanghai Municipal People’s Government, 2020c).
2.5.2.3 Recovery
Policies for foreign-funded enterprises’ recovery included three aspects (Shanghai Municipal
People’s Government Information Office, 2020). First, through the official website of the
Commerce Commission, WeChat official account, etc., publicity was carried out to help
foreign-funded enterprises understand COVID-related policy. Second, implementing the
policy benefited more than 140 foreign-funded enterprises and three key foreign-funded
epidemic prevention material production enterprises. Third, taking advantage of the
geographical advantages of the Yangtze River Delta helped foreign-funded enterprises resume

work and production through government-guaranteed food, raw material supply, and
transportation
logistics.
Shanghai adopted two strategies to secure the provision of vegetables (Shanghai Municipal
People’s Government Information Office, 2020). For one thing, Shanghai strengthened the
replanting of green leafy vegetables. From February 2020 onward, 30,000 mu9 of green leafy
vegetables were sown. At the same time, 15,000 kilograms of high-quality vegetable seeds
were supplied to meet the demand for rushed planting. The government also coordinated with
enterprises to guarantee vegetable production and marketing. In February 2020, 118
cooperatives, enterprises, and other institutions in nine agriculture-related areas launched
order delivery services for vegetables and other agricultural products (Shanghai Municipal
People’s Government Information Office, 2020).
On April 8, the General Office of the Shanghai Municipal Government issued the “Shanghai
Action Plan for Promoting Online New Economic Development (2020-2022)”. The "Action
Plan" mentioned 12 key development areas, roughly divided into three categories. First, new
businesses and models were spawned due to the pandemic, including telecommuting and
“contactless” delivery. Second, the Action Plan integrated online and offline formats such as
exhibitions, education, and medical care. Third, Shanghai incubated unmanned factories and
the industrial Internet through big data, online entertainment, fresh food e-commerce retail,
and other formats, as the public demanded online content to replace previously operated face-
toface systems (General Office of the Shanghai Municipal Government, 2020). The plan,
9 Mu is a Chinese measure of land area. 30,000 mu is approximately 7.72 square miles.

formulated by the General Office of the Shanghai Municipal Government in 2020, was
strategically developed to adapt to fluctuations in production, life, and consumer demand
during the epidemic. It aimed to foster new economic scenarios and momentum, thereby
supporting epidemic prevention and control measures while simultaneously facilitating
economic transformation and resilience in response to the ongoing public health crisis.
2.6 Analysis
As shown in Table 2.3, the factors for successful policy implementation differ between Henan
Province and Shanghai. Henan and Shanghai had clear goals for the COVID response derived
from the central government. With sometimes crude commutation and actions, Henan paid
more attention to the central government’s orders with a conservative strategy. At the same
time, Shanghai accepted the ideas of specialized bureaucrats and implemented the COVID
response through internationalization and openness. Henan focused on protecting vulnerable
people and emphasized stricter COVID-19 response strategies. Shanghai aimed to fulfill the
goals of both epidemic prevention and control and support the national economy through
“precise control.”10 Henan consistently implemented policies that closely aligned with the
directives from Beijing. This strict compliance was evident in their public health strategies,
lockdown measures, and the mobilization of resources, which were all in line with the central
10 Officials in Shanghai used the term “precise control” to advance methods uniquely
directed to specific, local conditions and minimize generalized “one size fits all” approaches
(You, 2021).

government’s guidelines. Henan's approach was characterized by a top-down enforcement,
where local authorities strictly followed the playbook provided by the central leadership.
Shanghai, while not defying the central government's orders, demonstrated a more nuanced
approach. Leveraging its unique status as a global financial hub and a city with significant
international influence, Shanghai exercised a certain degree of discretion in interpreting and
implementing these directives. This autonomy is rooted in the city's historical and economic
significance, which has afforded it a degree of latitude in administrative and policy decisions.
Shanghai's response to the pandemic, therefore, was marked by a balance between adherence
to national strategies and a more flexible, localized approach.
As shown in Table 2.4, the Chinese characteristics of COVID response in policy
implementation also differ from the theoretical models derived from Western countries (1975,
1976). These deviations are particularly evident in three key areas: communication factors,
disposition factors, and capabilities. When considering communication factors, the policy
objectives within China are characterized by a greater level of precision and clarity, especially
when comparing the coherence and consistency between central and subnational government
directives to those observed in Western nations. This clarity is crucial in the Chinese context,
where the alignment of goals and actions across different levels of government is paramount.
Furthermore, the communication strategies employed by Chinese authorities are heavily
focused on the maintenance of social stability, which is perceived as a fundamental pillar for
ensuring national cohesion and order. This emphasis is rooted in the belief that a stable
society is essential for the prosperity and longevity of the state. Moreover, there is a
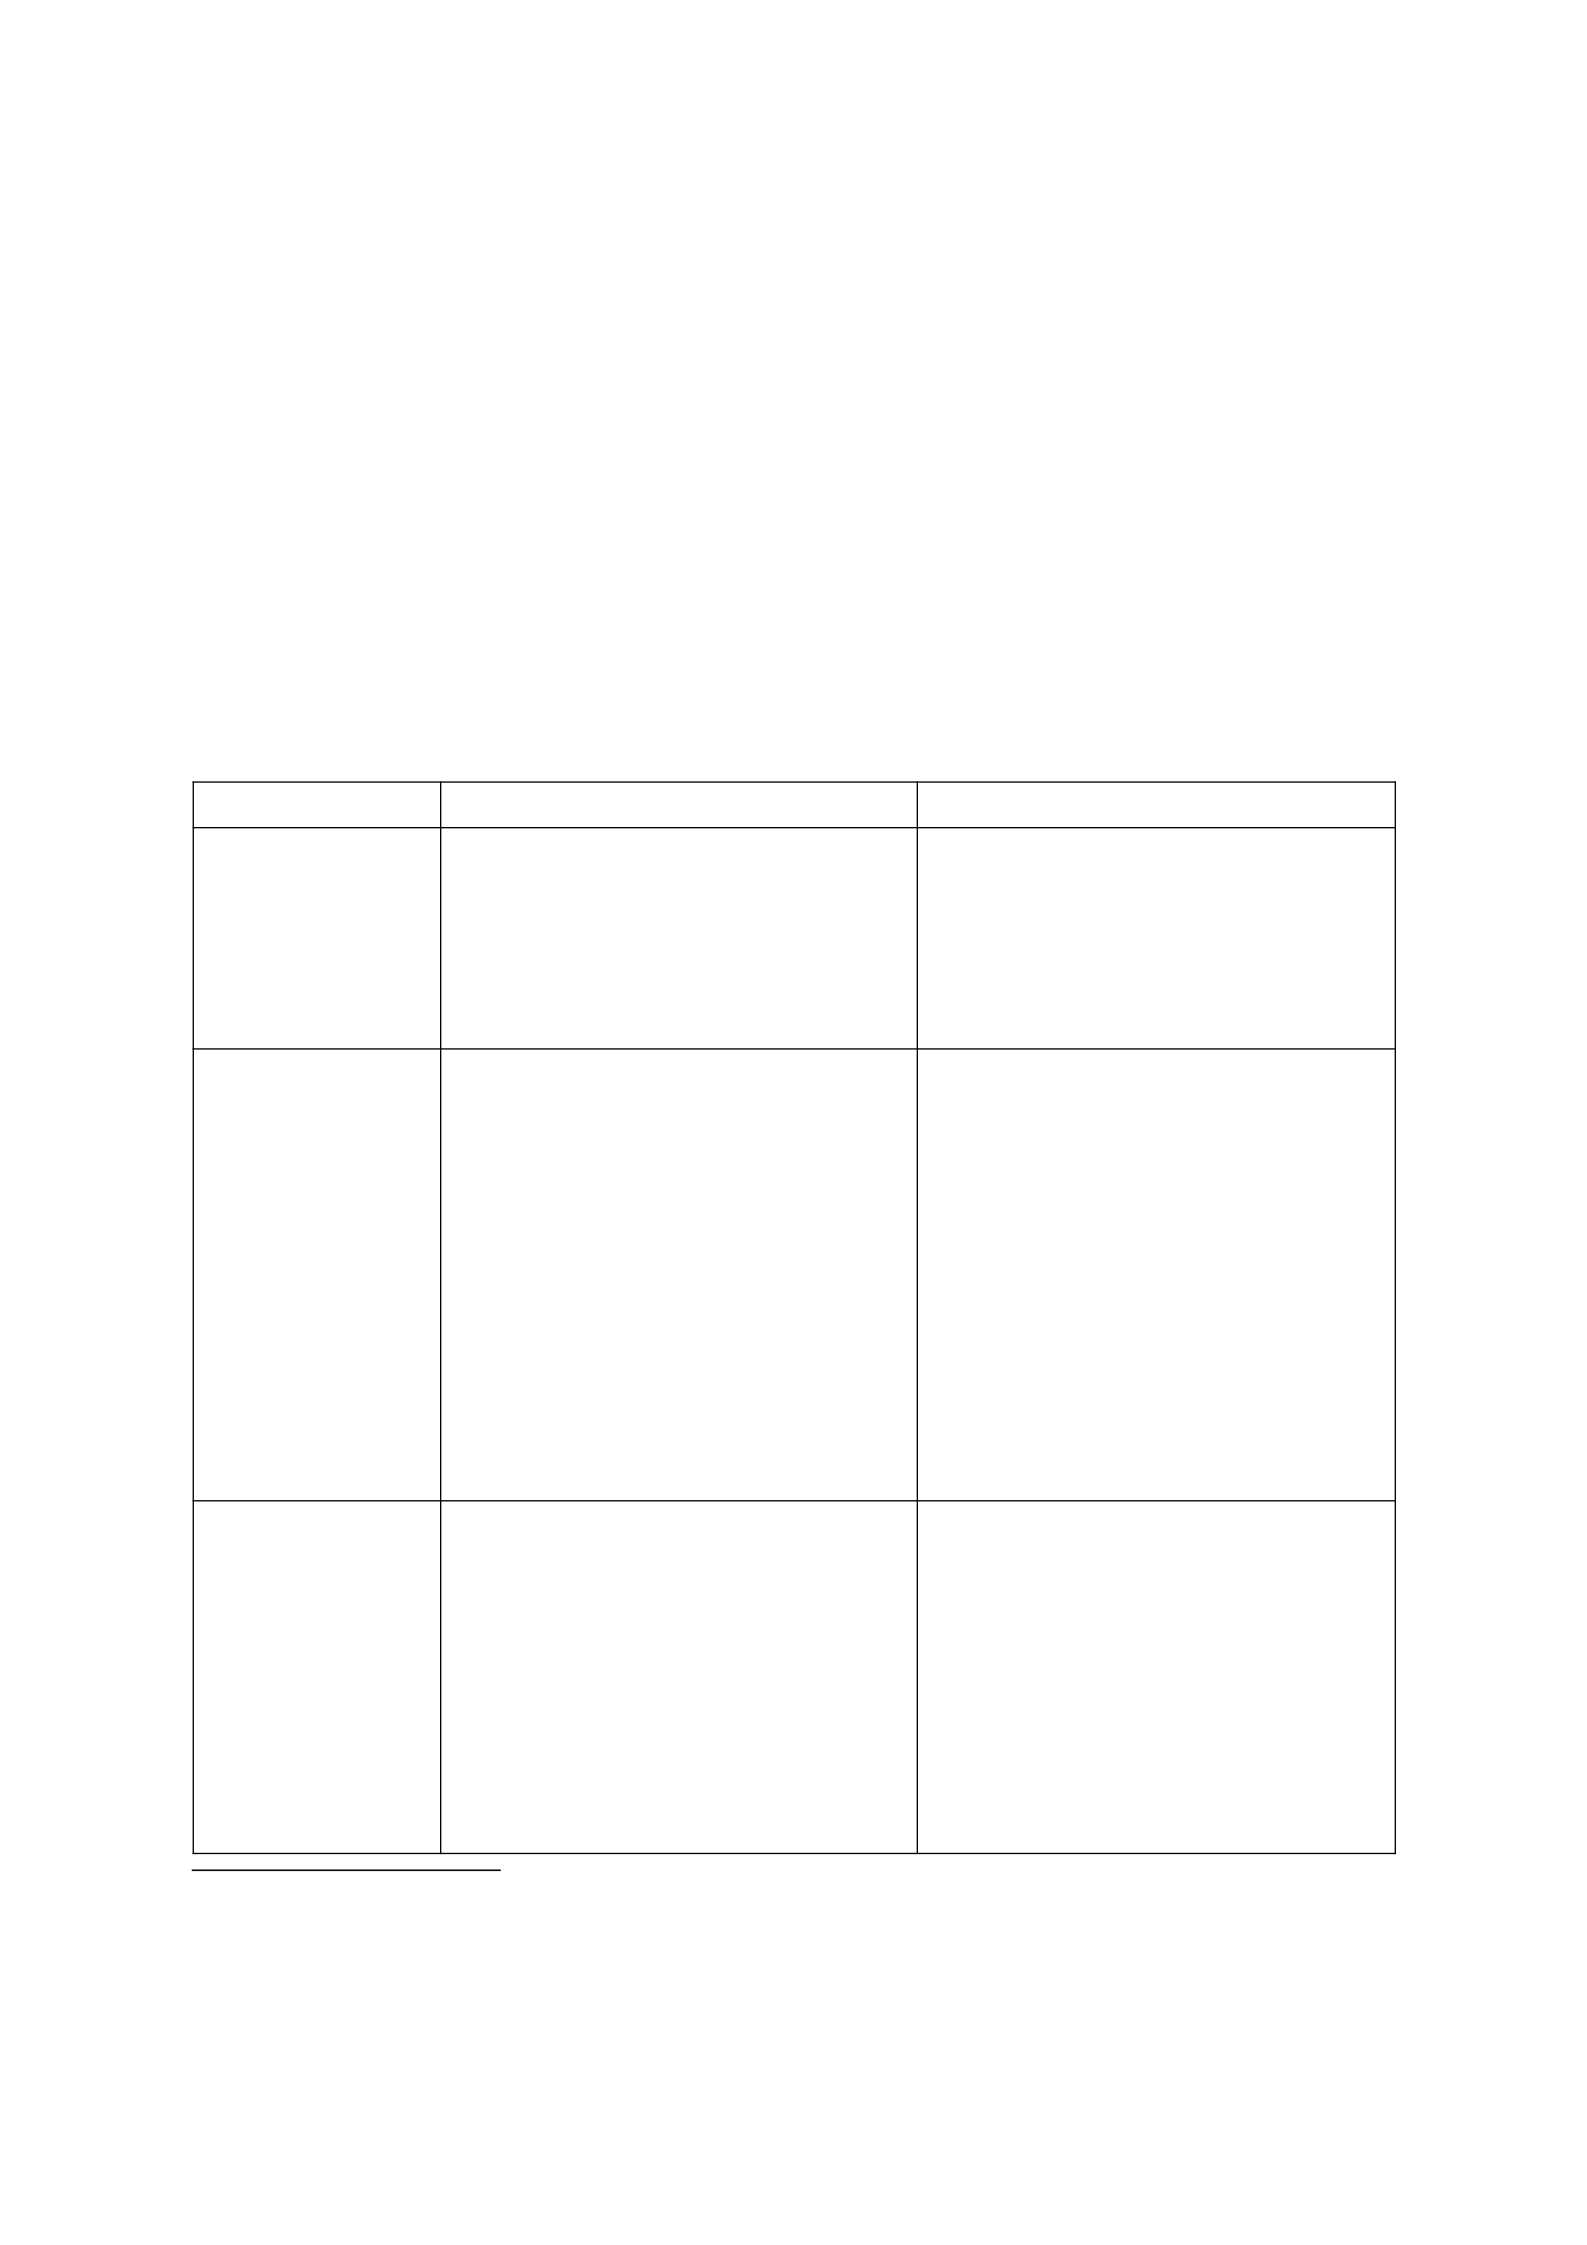
pronounced focus on enhancing political performance, which is often assessed in terms of
economic growth and the achievement of social harmony. These factors are not only vital for
the general well-being of the populace but also play a crucial role in the advancement of
officials' political careers within the hierarchical party-state structure. The effective
management of these aspects is seen as a key indicator of leadership capability, significantly
influencing the prospects for promotion and advancement within the government.
Table 2.3 Comparison between Henan and Shanghai’s Factors for Their Policy
Implementation
Henan Shanghai
Communications Clear goals of COVID response
derived from central government.
Protect Vulnerable people
Clear COVID Policy
Clear goals of COVID response
derived from central government.
Secure economic development
through “precise” epidemic
prevention and control
Dispositions Strictly obeyed the requirements of
the central government.
The central government’s order
played a critical role.
Conservative Strategy with
Sometimes Crude
Communications and Actions11
Paid more attention to central
governments’ orders and
requirements.
Followed major government
orders, but with some discretion
Relied on its autonomous
characteristics to prevent
epidemics
Internationalization and Openness
The government accepted the
ideas of specialized bureaucrats in
the COVID response.
Capabilities Difficulty in resource distribution
due to scattered population.
Public Resources and
administrative competencies lag
behind the coastal region of
China.
Openness leads to vital information
acquisition and learning.
Advanced medical techniques and
public health resources.
High efficiency in the allocation of
public resources due to the
centralized distribution of urban
districts.
11 For example, government communications sometimes employed crude threats of possible
consequences, and interventions sometimes included digging up rural roads to inhibit travel.

Regarding disposition factors, the dynamic in China differs markedly from Western models.
Provincial leaders in China typically have very limited discretion in deviating from the central
government's mandates. The emphasis is placed heavily on demonstrating loyalty and
unwavering adherence to the directives issued by higher authorities. This contrasts with the
Western approach, where subnational leaders often have more room to maneuver and adapt
policies to local contexts. In China, the expectation is that provincial leaders not only follow
the central directives but also actively work to ensure their successful implementation,
reflecting a top-down governance structure.
In terms of capabilities, the Chinese model places a significant emphasis on the role of
provincial governments in interpreting and implementing orders from their supervisors. This
aspect is critically different from Van Meter and Van Horn’s model, which acknowledges a
more substantial role for civil society and third-party actors in policy implementation. In
China, the relative weakness of civil society and the dominance of the national government
limit the influence of non-governmental actors in the policy process. Consequently, the
effectiveness of policy implementation in China is heavily dependent on the administrative
capacity and compliance of provincial governments.
Table 2.5 depicts how Henan and Shanghai created unique approaches. Both Henan and
Shanghai adopted COVID strategies in a similar perspective. In the preparedness phase, each
province focused on controlling the source of infection, protecting vulnerable groups, and
cutting off transmission routes. They also continued to work on providing stable resources for
public health and daily materials. The two provinces adopted financial and policy strategies to

assist citizens and various organizations and reduce financial burdens on state-owned and
private enterprises. Both Henan and Shanghai adopted varied approaches to respond to
COVID-19, tailored to unique circumstances where their policy implementation factors such
as local economic conditions, healthcare infrastructure, and public compliance levels
significantly differed.
2.6.1 Communication Factors
According to Van Meter and Van Horn (1976, 466), the critical issue in communication
factors is clear policy objectives and goals based on accurate and consistent communication.
The essential part relates to top-management support. As for communication factors in the
Chinese context, with solid backing from top management, the objectives are relatively
straightforward for provincial leaders to understand. On the one hand, the goal of government
officials is to pursue better performance and gain recognition from their superiors for career
purposes. On the other hand, maintaining loyalty to higher-level officials has always been a
central theme, and strict compliance with the instructions of higher-level government is an
essential factor in evaluating officials. In addition, maintaining social stability and harmony is
also a critical assessment indicator for Chinese government officials.
For Henan Province, those aged 0-14 number 23 million, accounting for 23.14% of the
population; the population over 65 years old is 13.41 million, accounting for 13.49% (Henan
Province Bureau of Statistics, 2021b). The 36.63% proportion of vulnerable people made
epidemic prevention an urgent issue for Henan Province. Due to the relatively high
proportion of susceptible people and the vast population base, strengthening protection was
the primary goal. It was necessary to prevent the spread of the epidemic quickly. In addition,
the Henan provincial government’s attitude towards higher-level authorities showcased their
deference, reflecting a commitment to following the instructions and leveraging the support
offered by the upper-level government to navigate through administrative and crisis
challenges.
Table 2.4 Comparison between Chinese Characteristics Mechanisms of Policy
Implementation and Western Context
Factors Chinese Characteristics of Policy
Implementation in COVID
Response
Policy Implementation borrowed
from Van Meter and Van Horn
(1975 and 1976)
Communications Clear policy objectives and
accurate and consistent
communication.
Explicit top-management support.
Maintenance of social stability.
Emphasis on political
performance. Promotion in
officials’ political careers.
Understand what needs to be done
by policymakers.
Political goals (re-elections,
reappointment, maintenance of
power, appearing legitimate, etc.)
Policy goals (adopting beneficial
policies and attracting large tax
bases to underwrite government
activities)
Dispositions Provincial leaders had no chance
to disobey the orders from the
central government.
Loyalty and close attention to the
central government are
compulsory.
Individual opinions and
experiences.
Supervisors’ attitudes.
Dispositional conflicts occur
because subordinates reject the
goals of their superiors.
Individual opinions and
experiences.
The Desires of the electorate,
interest groups, etc.
Capabilities Pay more attention to interpreting
and implementing supervisors'
orders (Xiang, 2023).
Adequate preparation
toward limitations and
problems.

Shanghai accelerated epidemiological investigations and conducted standardized procedures
for epidemic prevention, thereby completing “dynamic zeroing”12 in a way that had the most
negligible impact on social life and economic development (You, 2021). In the face of sudden
COVID-19, ensuring public safety became a priority. At the same time, most inland cities
suffered economic decline under the influence of city closures. According to Zheng (2022),
this delicate balancing act involved implementing stringent epidemic prevention and control
measures alongside initiatives aimed at stimulating economic activity. This strategy
underscored the necessity of ensuring public health and safety without compromising
economic growth, highlighting the city's innovative approach to navigating the complex
interplay between maintaining health security and supporting economic resilience.
Facing these situations, Shanghai carried out epidemiological investigations, isolation control,
and nucleic acid screening to improve the efficiency of epidemic prevention and gain more
time and workforce to ensure local and national economic development (You, 2021).
Specifically, after the emergence of new cases, the Shanghai Municipal Government and its
subordinate departments, including public security, communications, civil affairs, and
transportation, traced suspected and confirmed cases within 24 hours (You, 2021).
To fulfill these goals, Shanghai shortened the transmission route of cases through
collaboration with social organizations such as enterprises, universities, hospitals, and big
data centers to control the virus in the corresponding area and reduce the impact on society
12 “Dynamic zeroing” was a set of overlapping strategies intended to achieve zero COVID
cases (Llupia et al., 2020).

(Xue, 2021; You, 2021). The "Shanghai model" is a strategic government approach focused
on quick, efficient epidemic containment, utilizing forward-looking measures and cross-
sector cooperation to significantly reduce the epidemic's impact. This model exemplifies
Shanghai's capability to swiftly address public health challenges, highlighting a strong
commitment to comprehensive, effective response strategies. This example showcases the
city's proactive and coordinated approach in managing crises, emphasizing public safety and
health resilience. The strategy involves systematic planning and multi-sector collaboration,
engaging healthcare, public services, and community organizations to mitigate risks
effectively and ensure a comprehensive response to emergencies, enhancing overall
community safety and health.
2.6.2 Dispositional Factors
The dispositional factors relate to the conflictive relationship between subordinate
governments and their superiors because of loyalties, personal values, and alternation of
organizational procedures. In the Chinese context, provincial/municipal leaders’ loyalty and
strict obeyance toward the central government becomes critical. They also need to keep
focusing on the central government’s dynamic to ensure they can understand them clearly. On
the one hand, the State Council and the Health and Medical Commission insisted that the
policies of the higher authorities be strictly enforced. In addition, Henan and Shanghai paid
attention to the dynamics of other provincial governments. For instance, they learned the
lessons of Hubei Province’s failure in the COVID response, marked by its high number of
confirmed cases (Shi, 2020). COVID-19 has been a test for government officials in various
provinces in China. Those who performed poorly were dismissed (for example, in Hubei
Province). At the same time, individuals who demonstrated exceptional skills in emergency
response and governance capabilities not only received positive public recognition but also
laid a solid foundation for the promotion of their political careers in the future. This
acknowledgment served as a powerful catalyst for future opportunities, significantly
enhancing the profiles and credibility of those recognized within the political sphere. It paved
the way for advancement and increased influence, marking them as key figures in future
political and governance discussions (Myers, 2020; Yang, 2020).
Table 2.5: Cross-Case Comparison of COVID Strategies Implemented by Henan and
Shanghai
Henan Shanghai
Preparedness Similar strategies:
Protection of vulnerable groups
(young and old)
Cut off traffic with Hubei
Strengthen material reserves
Discrepancies in implementation:
Roads were cut off in the villages’
lockdown
Blunt publicizing epidemic
information
Similar strategies:
Material storage and mobilization
Improving the equipment of medical
staff, equipment, and medicines
Control traffic arteries and public
places
Check suspected cases
Discrepancies in implementation:
Classified publicity based on the
characteristics of citizens
Response Similar strategies:
Close public places and scenic spots
Classified management of
intraprovincial and inter-provincial
material delivery vehicles
Provided diversified
medical treatment for various
patients. Discrepancies in
implementation: Protected the rights
and interests of migrant workers.
Similar strategies:
Close scenic spots and public places
Saved the COVID patients with
concentrated medical experts.
Improvement of medical technology
Discrepancies in implementation:
“Precise prevention and control”
through AI and significant data flow
investigation.
Focused on economic guarantee and
epidemic prevention concurrently
Emphasized the role of specialized
bureaucrats in epidemic prevention.
Recovery Similar strategies: Similar strategies:

Supported the resumption and
production of enterprises through
economic policies.
Operated Health QR code of Henan
for epidemic prevention and control.
Discrepancies in implementation:
Accelerated mobilization of labor
force.
Industrial chain resumption of work
and production linkage.
Discrepancies in implementation:
Supported the resumption
and production of foreign
enterprises through specialized
policies.
Incubated new industries during
COVID-19 to guarantee economic
recovery.
The disposition of policymakers usually combines their attitudes and governance experiences
with the views of their superiors' goals as well as those of the public and interest groups.
Thirdparty organizations (e.g., social organizations, hospitals, and policy entrepreneurs) in
Western countries can express their opinions on important matters. However, China is state-
centered and relies on a top-down policy system with government-led partnerships. Third-
party organizations in China have limited power to express their views. To cooperate with the
government, they need to influence the selection of government officials and usually
collaborate under the guidance of government officials, reflecting the core characteristics of
obedience and service (Freedom House, 2020; Xiang, 2023). The inherent power imbalance
in China makes it relatively easy for all levels of government to command the go-betweens,
including professional bureaucrats, social organizations, and citizens. When governmental
officials ask them to adapt to and promote network governance, participants generally dare
not slack off or oppose them (Xiang, 2023). Therefore, under a centralized system,
dispositions are primarily determined by the attitudes and requirements of higher-level
government and the prominent leaders’ perspectives and administrative experiences (Xiang,

2023). It is difficult for external actors to express their views on public affairs to government
officials, and it is even more difficult for their ideas to be adopted.
Henan Province strictly implemented COVID response policies required by the State Council
and the National Health Commission. Governor Yin Hong stated that, if necessary, those in
charge of the central government’s joint defense and joint control mechanism could direct the
COVID response work of the provincial party committee and the local government (Wang,
2020). Yin was thus signaling his loyalty to the central government. This also indicated that
the central government in China strongly influences the subnational governments.
With more than 44 million rural citizens, Henan Province is also China’s most populous
inland agricultural province (Henan Province Bureau of Statistics, 2021a). In borrowing and
formulating epidemic prevention policies, it was inclined to adopt more restrictive
implementation policy models (He, 2020; Yang, 2020). Learning from failures in Hubei,
Henan
Province adopted exaggerated means to control the pandemic. For instance, some areas of
Henan dug up sections of rural-level transportation lines to Hubei Province (He, 2020; Yang,
2020; Zhang, 2020). Also, publicity in China's rural areas is often characterized by billboard
advertisements, frequently reflected during the epidemic. Street-level bureaucrats in Henan
carried out anti-epidemic propaganda to rural people through simple, crude, and well-
organized slogans combined with loudspeaker broadcasts (Wu, 2020). These simple and
direct measures appear clumsy, but they sometimes deter less-sophisticated rural citizens who
were still afraid of the unprecedented virus and the sense of horror brought by the increasing

number of confirmed cases. The role of external participants in Henan Province was weak,
for the provincial government strictly listened to the central government’s requirements and
COVID response strategies provided by the National Health Commission.
It appears that Shanghai relied on its administrative system to achieve policy successes, and
its
“precise” prevention and control practices were learned and emulated from other provinces.
Following Yan (2015), I assume that Shanghai benefitted from having its top officials seated
in important central government committees. As a municipality directly under the central
government, it is likely that other governments closely observe its actions. If the policies
formulated and implemented in the policymaking process are effective, they are more likely
to be considered role models by the central government and other provinces. Unlike most
interior provinces’ strict lockdown policies, Shanghai avoided copying their “one size fits all”
strategies.
Instead, Shanghai coordinated economic development with the COVID response by
implementing “precise control” policies. Thus, after the 1st quarter of 2020, most Chinese
cities faced the governance challenges of coordinating complicated affairs concerning public
health management and economic development. While focusing on their situations, these
governments could learn from the “Shanghai Mode”14 as a possible reference (Yang, 2020).
Shanghai became China’s earliest treaty port in the 1840s Sino-British war and has been open
to the world for approximately 180 years13. The early influence from the Western world and
13 Treaty of Nanking (1843) required Qing Government to open Guangzhou, Xiamen,
Fuzhou, Ningbo, and Shanghai as commercial ports for The United Kingdom.

the Chinese Economic Reform14 made Shanghai an internationalized city. Thus, Shanghai
advocated scientific, refined, and international governance models. Different from the “one
size fits all” and more extensive prevention and control approaches of inland provinces,
Shanghai paid more attention to the efficient use of public resources such as people, property,
and materials brought about by “precise” prevention and control to balance epidemic
14 The so-called regional epidemic prevention models include the Wuhan model during the
outbreak period, the Beijing model in sporadic cases, and the Shanghai model for dealing
with imported sporadic individual cases.
prevention and control with economic and social development. Therefore, within one month of
starting its first-level response to the public health crisis, on February 17, 2020, the Shanghai
Municipal Government emphasized the newly invented local mobile client “Shanghai QR
Code” to accurately register the movement trajectories of people and realize the scientific
allocation of epidemic prevention resources (“Three-color dynamic Shanghai QR Code,”
2020).
Shanghai’s epidemic response strategy had international characteristics, and its “precise”
prevention and control were similar to epidemic prevention strategies adopted by Singapore
at the same time (Singapore Government Agency, 2020). Led by the government, Singapore
14 The Chinese economic reform or Chinese economic miracle, also known domestically as
Reform and Opening-up refers to a variety of economic reforms termed “socialism with
Chinese characteristics” and “Socialist market economy” in the People's Republic of China
(PRC) that began in the late 20th century (Ray, 2002; Harrison et al., 2019).

adopted a top-down strategy and DORSCON (Disease Outbreak Response System Status) to
control the pandemic 15 . DORSCON employed a system of four colors, for example, in
cellphone apps and websites, corresponding to four different severity levels in the spread of
the disease. Each level corresponds to other virus impacts and public epidemic prevention
advice (Singapore Government Agency, 2020). Similarly, Shanghai launched the “Shanghai
QR code” on February 17, 2020, using red, yellow, and green colors to classify citizens
according to their travel into higher COVID risk areas (Li, 2020). Singapore also identified
three recovery phases, Safe Restart, Safe Transition, and Safe Nation, with real-time
adjustments based on public
health (Wong et al., 2021). After the end of the first-level response, Shanghai also
experienced three recovery stages, including the containment + overall planning stage, the
normalized prevention and control stage, and the dynamic clearing stage.
Shanghai differed from Henan, which regarded the central government’s requirements and
strategies as a core tenet. The municipal government moderately valued the role of
professional bureaucrats. As the leader of the Shanghai Medical Treatment Expert Team,
Zhang Wenhong is a bureaucrat with a professional background in public health. Relying on
his scientific interpretation of domestic and international public health situations and his
15 DORSCON refers to “Disease Outbreak Response System Condition” (a color-coded
framework showing the current disease situation), which was first used during the 2009 swine
flu pandemic in Singapore. https://www.gov.sg/article/what - do - the - different - dorscon -
levels mean

unique and charismatic work style, his suggestions during the response to the epidemic
played an essential role in local government decision-making. They were generally praised by
society (Wu, 2020).
2.6.3 Capabilities Factors
This study suggests that strong and visionary political leaders can improve the quality of
policy implementation by setting ambitious goals, seeking possibilities for change, and
providing appropriate financial and personnel support for those policymakers. Also,
policymakers may collaborate with experts, stakeholders, and other governments to exchange
ideas, share best strategies, and learn from successful policies implemented elsewhere.
International organizations and networks facilitate such collaborations and can stimulate
policy implementation. Apart from these, in the Chinese perspective, the capabilities of local
governments in the process of policy implementation are reflected in the following aspects:
(1) The ability of government officials to understand and implement the spirit conveyed in
policies promulgated by higher-level government; (2) The experience and administrative style
of government officials themselves; (3) The ability of professional bureaucrats to integrate
their initiatives with government thinking; and (4) The operational efficiency of the
bureaucratic system.
Economic conditions, including resource availability, budget constraints, and cost-benefit
considerations, can influence the type and quality of policy implementation. COVID response
policies that are economically viable and demonstrate potential benefits are more likely to be
implemented. On the one hand, the overall economic level of Henan Province is not as good

as that of Shanghai. On the other hand, because Henan’s population is widely dispersed, the
provincial government experienced difficulties allocating public resources during the COVID
period. Thus, Henan could not conduct the same “precise” control of COVID-19 as Shanghai,
which requires more financial and personnel expenditures. Regarding hospital quality,
according to the 2020 China Hospital Rankings released by Fudan University, the top-ranked
hospital in Henan Province ranks 19th in China. Shanghai has three in the top ten, and 19
hospitals in Shanghai are in the top 100 in China. This suggests that Shanghai’s medical
services are among the best in the country (Hospital Management Institute of Fudan
University, 2020).
Technological progress can promote policy implementation by introducing and applying new
tools, approaches, and solutions to respond to emerging challenges or improve efficiency in
subsequent policy implementation. Shanghai is strong in virus research and tackling critical
problems and has achieved results in many COVID-related projects, including new drug
research, preliminary screening of COVID-19 samples, releasing anti-COVID compounds,
and isolating COVID-19 strains (Dang, 2020). Regarding disease prevention and control
systems, Shanghai introduced extensive data methods to trace the pathogen and categorize
suspected and confirmed COVID-19 patients (Gao, 2021). This contributed to developing and
applying basic research on etiology, drugs and treatment methods, monitoring and early
warning technologies, and vaccines (Gao, 2021). As one of China's most economically
developed regions, Shanghai has the top administrative and social management level in China

(Gao, 2021). These differences account for Henan and Shanghai's varied policy adoption and
implementation practices.
2.7. Conclusion
With the help of policy implementation and related knowledge of emergency management,
this manuscript compares the epidemic responses and recoveries in Henan and Shanghai in
the first half of 2020. This study draws the following conclusions by comparing the
communication, disposition, and capabilities factors of these two regions’ COVID response
policies. The policy implementation model with Chinese characteristics differs from the
Western context (see Van Meter and Van Horn, 1975. 1976). Also, when each province
responds to COVID-19, their unique contexts entail various factors, thus leading to different
policy outcomes.
This study also invites necessary extensions for future research. First, this study undertook
comparative studies in only two Chinese provinces/municipalities. Similar studies in other
settings can contribute to a more generalized understanding of these dynamics. For instance,
autonomous regions and other provinces can be examined in subsequent research. Second,
due to time, distance, lockdown policies, and the sensitiveness of COVID-19 topics in China,
it was not possible to conduct face-to-face interviews with administrative staff and citizens
who participated in epidemic prevention and control. If in-person interviews can be
undertaken, I would approach citizens, street-level bureaucrats, and lower-level medical staff
to explore the micro-level dynamics of the COVID response. Third, archival material that

provided the principal data for this study may also reflect biases similar to those noted in an
earlier manuscript about government leaders’ intentions to control social media and news
reporting
(Xiang, 2023). This problem is an ongoing challenge for this study and others conducted in
China and other countries with centralized or authoritarian regimes.
This manuscript makes several contributions to the field of policy implementation. Borrowing
these ideas derived from Van Meter and Van Horn’s (1976) model, this study exposes readers
to the differences between Chinese characteristic policy implementation mechanisms (Zhang
& Zhu, 2019; Tai et al., 2022) and parallel mechanisms often attributed to Western countries
(e.g., Van Meter and Van Horn, 1975 and 1976). Specifically, the current study shows readers
how detailed contextual factors can affect various governments’ COVID-19 policy
implementation strategies under the centralized system.
CHAPTER 3 MULTIPLE STREAMS FRAMEWORK IN US STATES
3.1 Chapter Overview
Utilizing the Multiple Streams Framework (MSF), this research delves into the determinants
guiding COVID-related decisions across U.S. states from August 2020 to January 2022. It
critically evaluates eight salient variables linked to the problem, policy, and political streams
of MSF, focusing on the adoption patterns of mask mandate policies. The analysis reveals that
factors such as monthly COVID-19 case rates, political affiliation, vaccination rates, and

interstate travel restrictions significantly influenced the strictness of mask mandates during
different periods.
Keywords: US COVID Mask Mandate, Policy Change, Multiple Streams Framework,
Policymaking, Policy Implementation
3.2 Introduction
Navigating the intricate policy-making environment during the COVID-19 pandemic,
particularly concerning mask mandates, this study poses a research question: Considering the
numerous influences on policy-making, how does the Multiple Streams Framework shed light
on the crucial determinants affecting the stringency of mask mandate policies?
In the kaleidoscope of policy genesis and deployment, especially about mask mandates amid
the COVID-19 crisis, the Multiple Streams Framework (MSF) is pivotal, unfurling insightful
revelations into policy decisions' oscillating and dynamic facets. Conceptualizing policies as a
convergence of three primary streams – problem, policy, and politics (Kingdon, 1984, 1995) –
MSF not only grounds itself firmly in the assessment of mask mandate policies curated by
states amidst the erratic nature of the COVID-19 pandemic but also demonstrates remarkable
adaptability in dissecting the undercurrents that have shaped such policies.
3.2.1 Justifying MSF’s Appropriateness
The MSF is appropriate as a theory to guide this inquiry due to its capacity to encapsulate the
intertwined dynamics of policy-making. During the COVID-19 pandemic, the ambiguity and

multiplicity of challenges accentuated the need for a model that could seamlessly integrate
various inputs, discern nuances, and navigate through the entangled web of urgent health
imperatives, myriad policy alternatives, and the politicized environment, which MSF
proficiently accomplishes.
3.2.2 Methodological Alignment with MSF
Analyzing the Problem Stream: Investigating the trajectory of the pandemic’s progression,
from initial outbreaks to peak crisis periods, necessitates evaluating how escalating infections
and mortality rates were perceived, internalized, and articulated within policy circles and
public discourse. Engaging in a temporal analysis of the articulation of the crisis and response
synchronization will illuminate how the perception of the problem was intertwined with
resultant policies.
Interrogating the Policy Stream: Exploring the stream demands meticulous navigation
through potential responses by systematically mapping out policy proposals, scrutinizing their
congruence or disparity with expert recommendations, and evaluating their implementation
and subsequent impact. A comparative and quantitative analysis will decipher the factors
influencing various degrees of mask mandate strategies across different states—from
comprehensive mask requirements to more permissive guidelines. This approach will enable
a nuanced understanding of the dynamics that catalyzed alterations in such degrees.
Delineating the Politics Stream: This exploration will involve situating policy choices within
the political narrative, discerning alignments or disjunctions with political ideologies, election
cycles, and policy legacies. It further demands an analysis of stakeholder influence, lobbying,

and advocacy, deciphering how these elements either facilitated or hindered the policy-
making and implementation process.
The meticulous intersection of these streams, rendered even more complex amidst the volatile
framework of the COVID-19 pandemic, underscores the pertinence of employing MSF. This
exploration will explore the mechanics and motivations behind developing and imposing
varied mask mandate policies across divergent states. By interweaving theoretical
frameworks with rigorous empirical investigation, this study aims not solely to comprehend
the complex policy dynamics at the heart of the current crisis but also to identify and
construct viable pathways that future policy-making efforts can navigate in dealing with
subsequent public health challenges. This approach ensures a robust foundation for
understanding and action, providing a comprehensive strategy to anticipate and manage the
intricacies of emergent health exigencies effectively.
3.3 Theoretical Framework and Background of US COVID Quarantine Policy
3.3.1 Multiple Streams Framework
According to Kingdon (2011), Multiple Streams Framework (MSF) can deal with ambiguity,
time constraints, problematic preferences, unclear technology, fluid participation, and stream
independence. Here, ambiguity refers to “a state of having many ways of thinking about the
same circumstances or phenomena” (Feldman 1989, 5). Differing from uncertainty, which
can be reduced by information mining, ambiguity cannot be reduced by increasing amounts

of information (Feldman 1989, 5). Time constraints arise because attending to or processing
events and circumstances in political systems can occur in parallel, whereas individuals’
ability to give attention to or process information is serial (Herweg, Zahariadis, &
Zohlnhofer, 2018). Because many issues require attention, policymakers feel that urgency is
occurring to force them to address them, thereby “striking while the iron is hot.”
Consequently, time constraints limit the range and number of alternatives given to attention
(Herweg, Zahariadis, & Zohlnhofer, 2018).
For problematic policy preferences, policymakers do not have clear preferences about specific
policies (Herweg, Zahariadis, & Zohlnhofer, 2018). Problematic policy preferences emerge
when ambiguity and time constraints emerge. How policymakers think about an issue
depends on its overarching label (e.g.: health, education, politics, morality, experience and
ideological preferences) and on the information that has been considered. Consequently,
actors’ policy preferences are not fixed but emerge during interaction (Herweg, Zahariadis, &
Zohlnhofer, 2018). Unclear Technology occurs when members of an organized anarchy know
only their responsibilities and exhibit only rudimentary knowledge of how their job fits into
the organization's overall mission (Herweg, Zahariadis, & Zohlnhofer, 2018).
For fluid participation, this can complicate the problems derived from unclear technology.
The composition of decision-making bodies is subject to constant change—either because it
varies with the concrete decision to be made or because turnover is high (Herweg, Zahariadis,
& Zohlnhofer, 2018). Stream Independence occurs when political problems, policy solutions,
and politics—referred to as problem stream, policy stream, and political stream—develop

independently (Herweg, Zahariadis, & Zohlnhofer, 2018). Because consensus building in the
political stream and the policy stream takes different forms, these streams also have their
dynamics (Kingdon 2011).
Ever since the formulation of the Multiple Streams Framework (MSF) by John Kingdon in
1984, the framework has acted as an efficacious heuristic tool for contemplating the evolution
of policy agendas and long-range stratagems for transformative changes by synergizing
societal problems, policy resolutions, and political dynamics (McLendon, 2003). Within the
framework of MSF, issues are perceived as deviations from an idealized situation, warranting
public acknowledgment of government intervention (Béland & Howlett, 2016). Based on
their practical applicability, many possible solutions are pinpointed, evaluated, and filtered in
the policy stream (Béland & Howlett, 2016). On the other hand, the political stream examines
mplications from the polity, encompassing elements like advocacy drives, legislative
alterations, and fluctuations in the political climate (Béland & Howlett, 2016). When the
streams above coalesce, they establish a 'policy window,' facilitating policy innovators and
responsive policymakers to forge beneficial linkages between a problem and its potential
solution (Herweg, 2016).
3.3.1.1 Problem Stream
Within the MSF, policy change begins with identifying the problem and agenda-setting.
According to Kingdon (1995), the process necessary to introduce a problem in the public
agenda is rooted in the interaction of the three streams. The conditions that deviate from
policymakers’ or citizens’ ideal states “are seen as public in the sense that government action

is needed to resolve them” (Béland and Howlett 2016, 222). Thus, problems contain a
“perceptual, interpretive element” (Kingdon 2011, 110) because people’s ideals and reality
vary significantly. In the problem stream, policymakers' perceptions are considered, as they
are the ones who need to assume a condition is a problem to develop a policy response.
Problems must lead to possible alternatives that produce solutions in particular policies
(Ruvalcaba-Gomez et al., 2023). In many situations, to be considered a problem, the issue
may need to have visibly captured social and political attention. The insertion of a problem
into a political agenda is frequently accomplished after a cluster of interrelated issues, which
are experienced across various societal sectors, converge, highlighting the systemic nature of
the problem (RuvalcabaGomez et al., 2023). This convergence of factors helps to elevate the
issue's visibility and urgency, prompting policymakers to prioritize it amidst a broader array
of competing interests and demands. By highlighting the critical nature of the problem, it
encourages swift and decisive action from decision-makers, ensuring the allocation of
necessary resources and attention.
3.3.1.2 Policy Stream
The policy stream of the MSF focuses on assessing policy solutions for existing problems,
bringing them to the forefront of agenda-setting frameworks. The policy stream is linked to
ideas and solutions, where actors present alternative actions that respond to the problem. In
this stream, it is assumed that subject experts search for solutions to the problem. Among
them, one may find scholars, consultants, and officials with experience or knowledge of the
issue (Ruvalcaba-Gomez et al., 2023). Policy alternatives are generated in policy

communities. A policy community “is mainly a loose connection of civil servants, interest
groups, academics, researchers and consultants (the so-called hidden participants), who
engage in working out alternatives to the policy problems of a specific policy field” (Herweg
2016, 132).
3.3.1.3 Political Stream
The MSF's politics stream comprises factors influencing the body politic (Béland & Howlett,
2016). These factors include swings in national mood, governing party turnover, and
advocacy campaigns of special interest groups (Béland & Howlett, 2016). Kingdon identified
three core elements in the political stream: the national mood, interest groups, and
government. The national mood is the most empirically elusive of these elements. This
elusiveness has led some researchers to dismiss it as an analytical category (Zahariadis,
1995). Interest group campaigns are the second element of the political stream (Herweg,
Zahariadis, & Zohlnhofer, 2018). Governments and legislatures, which change in
composition, constitute the third element of the political stream (Herweg, Zahariadis, &
Zohlnhofer, 2018). Following Kingdon’s theory (1995), the most salient factors guiding the
configuration of politics appear as follows: First, changes in governments and public
administrations play a pivotal role, as shifts in leadership and policymaking bodies can
drastically alter political priorities and strategies. Secondly, the activism of pressure groups is
a significant force, as these entities work tirelessly to influence policy through advocacy,
campaigning, and lobbying. Lastly, the broader political environment, including the
ideological climate and public opinion, forms an essential backdrop against which political

decisions are made and enacted. These elements collectively dictate the configuration of
politics, guiding the direction and focus of governmental action and policy development.
3.3.1.4 Agenda/Policy Window
Agenda windows are rare (at least about a particular policy proposal) and ephemeral; they can
be predictable (elections, budgets) or unpredictable (disasters) (Herweg, Zahariadis, &
Zohlnhofer, 2018). They can open in two streams: the problem or the political stream. A
window in the political stream opens if the partisan composition of government changes or
new members enter the legislature. Similarly, a significant shift in the national mood can open
an agenda window. In contrast, an agenda window opens in the problem stream when
indicators deteriorate dramatically.
3.3.1.5 Policy Entrepreneurs
These are “advocates who are willing to invest their resources (time, energy, reputation, and
money) to promote a position” (Kingdon 1995, 179). The promoters of specific demands or
advocates of the proposals in a focused event take advantage of the coupling of the three
streams. These actors are known as “policy entrepreneurs.” They are “advocates willing to
invest their resources—time, energy, reputation, money—to promote a position in return for
anticipated future gain in the form of material, purposive, or solidary benefits” (Kingdon
2011, 179).
3.3.2 Federalism in the U.S. and Its Relationship with the State-Level Response to COVID

Federalism, inherently designed to allocate powers amongst multiple self-governing entities
within a shared political sphere, provides a lens to comprehend the complex governmental
response to the COVID-19 pandemic in the United States (Karmis & Norman, 2005).
Interestingly, the nature of federalism witnessed nuanced dynamics under the Trump
administration (2017-2021), particularly illuminated during the COVID-19 pandemic. In
2020, the management of the pandemic became distinctly multifaceted and at times
contradictory, with the federal government, traditionally expected to manage nationwide
crises such as natural disasters and pandemics, delaying critical actions and federal agencies
navigating challenges posed by presidential interferences (Yamey, 2020; Tuccille, 2020).
Trump's approach to federalism during this period manifested a paradox: on the one hand, it
seemingly sought to diminish the federal government’s role, and on the other, it aimed to
augment presidential power, sometimes infringing upon state jurisdictions (Selin, 2021;
Goelzhauser & Konisky, 2020). Thus, the United States experienced a decentralized response
to the pandemic, wherein the states primarily shouldered the responsibility of managing the
crisis despite varying capabilities and resources, yielding a spectrum of strategies and
outcomes that warrants a detailed examination.
In contrast, the Biden administration's approach to federalism and pandemic management is
gradually unfolding and draws attention to the measures adopted by the federal government
to mitigate COVID-19 impacts and elevate public health initiatives (DaCosta et al., 2021;
SeitzWald, 2021). Importantly, even amidst the orchestration of a national policy framework,
the state-level responses under the aegis of federalism have been pivotal and varied. This

intricate interplay between national policy and state-level implementation provides a
fascinating context for analysis, elucidating the capacities and limitations embedded within
the federal framework during public health crises, thereby validating the significance and
interest in this research inquiry.
In sum, The COVID-19 pandemic in the U.S. showcased the challenges of federalism under
Trump and Biden's contrasting administrations. Trump's tenure marked a paradoxical
reduction in federal crisis management roles, leading to a decentralized response and varied
state strategies due to presidential interference. Conversely, Biden's approach emphasized
coordinated federal actions to combat the pandemic, though state responses remained vital
and diverse. This situation underscores the critical importance of federal impact analysis,
particularly as federal decisions have significantly influenced the overall pandemic response
within the intricate U.S. federal system. It highlights the complex interplay between national
directives and state-level implementations in managing public health crises. Conducting such
analysis is vital not only for evaluating the strengths and weaknesses of the federal response
but also for identifying effective strategies and areas needing improvement. This
understanding aids in refining coordination mechanisms and policy measures, ensuring that
future public health crises are managed more effectively and efficiently, with improved
outcomes at both the national and state levels.
3.3.3 Background
Due to a delayed response to the pandemic, the United States swiftly became one of the
countries most profoundly affected by the outbreak. The impact of the virus varied

considerably across states, owing to a confluence of factors encompassing population density,
age distribution, social determinants of health, and the timing and efficacy of public health
interventions. By April 2020, the United States had recorded the highest number of confirmed
cases and fatalities worldwide This distressing statistic has persisted, albeit with fluctuating
severity, throughout the pandemic. Various policies have been implemented during the
COVID-19 pandemic, including the enforcement of mask-wearing, shelter-in-place orders,
social distancing measures, illness-related quarantining, and widespread testing (CDC 2020;
Cohen and Kupferschmidt 2020; Fowler et al. 2020).
The response of public health authorities and the government to the pandemic in the United
States has been intricate and multifaceted, encompassing a range of measures such as
mandates for social distancing, closures of businesses and educational institutions,
requirements for wearing masks, extensive testing initiatives, and vaccination campaigns. In
January 2020, the U.S. Federal Government declared a public health emergency, prompting
subsequent actions by state governments to mitigate the COVID spreading (U.S. Department
of Health and Human Services, 2020). However, despite widespread vaccination efforts, the
United States continues to grapple with challenges, including disparities in vaccine
distribution, vaccine hesitancy, and the emergence of novel virus variants. These challenges,
along with the enduring repercussions on healthcare systems, the economy, and social
structures, continue to shape the ongoing response and recovery endeavors of the United
States about the COVID-19 pandemic as of the most recent update in September 2021.
According to the Multiple Streams Framework (MSF), COVID-19 brought the problem,

policy, and political streams together by creating a window of opportunity for policy change
and action. The convergence of these streams occurred as the severity of the COVID-19 crisis
became evident, and the need for a coordinated policy response became increasingly urgent.
They appear as follows:
3.3.3.1 Problem Stream during the COVID-19 Pandemic
The problem stream pertains to recognizing and framing an issue as a problem requiring
attention and action. The emergence of COVID-19 as a global health crisis posed a
substantial threat to public health and society. The fast transmission of the virus, escalating
infection rates, overwhelmed healthcare systems, and mounting mortality rates collectively
generated a sense of urgency and consensus that immediate action was imperative.
During the COVID-19 pandemic, framing the problem encompassed individual health, public
health, and economic impacts as interconnected elements within a single comprehensive
frame. This integrated approach, informed by the Multiple Streams Framework, recognized
the multifaceted nature of the crisis, necessitating policies that addressed both health and
economic well-being simultaneously. This situation underscored the importance of a holistic
view for effective policy development and implementation, reflecting the interdependence of
health and economic sectors in public decision-making. Such a comprehensive approach
ensures that policies are robust and adaptive, capable of addressing complex challenges by
integrating multiple perspectives and expertise.
3.3.3.2 Policy Stream during the COVID-19 Pandemic

The policy stream involves the development of potential solutions and policy proposals to
address the identified problem. In response to the COVID-19 pandemic, experts,
policymakers, and public health agencies collaborated to identify and formulate policy
options to mitigate the crisis's impact. These measures encompassed testing strategies,
vaccine development, formulation of social distancing guidelines, and implementation of
economic relief packages. Observers expect that existing health policies, such as a state’s
existing applications of Medicaid and Medicare policies, will affect the policy stream in the
future.
3.3.3.3 Political Stream during the COVID-19 Pandemic
The political stream encompasses the political environment, including public opinion, interest
groups, and the prevailing political context. The advent of COVID-19 created a highly
politicized atmosphere owing to its profound public health, economic, and social
ramifications. Political leaders and policymakers were pressured to mount effective responses
to the crisis, navigate public sentiment, manage the financial repercussions, and strike a
balance among the divergent demands of various interest groups.
During the COVID-19 pandemic, mask mandates in the United States were primarily
enforced at the state level. Each state possessed the authority to implement and enforce its
mask mandates, resulting in variations in enforcement methods across states. These methods
encompassed diverse approaches such as public awareness campaigns and educational
initiatives, involvement of law enforcement agencies, imposition of fines and penalties,

utilization of travel declaration forms, coordination with transportation providers, and
reliance on voluntary compliance and community cooperation.
3.4 About the Study and Hypotheses
The units of analysis for this study comprise the mask mandates of the 50 states, as the
response to COVID-19 in the United States has been primarily driven by state governments
(Curley,
2021). Given the rapid evolution of the situation throughout 2020 and the dynamic situation
in 2021, mask mandates were frequently adjusted in response to changing trends of COVID-
19 and guidance provided by public health officials in various states. Consequently, the
specific measures implemented and their durations varied over time and across different
states. By examining various factors, this study aims to identify the critical determinants
influencing states' policy adoption regarding the strictness of mask mandates.
This study uses state policies for mask mandates and vaccinations during COVID as the
dependent variable. The categories contain three policy decisions state governments could
take, including 1) the Mask requirement started, 2) fully vaccinated individuals were exempt,
and 3) the Mask requirement ended. The CDC initially advised using non-medical facial
masking in public to mitigate the spread of virus in the United States on April 3, 2020,
complementing hygiene and suitable social distancing practices (Sherman & Swann, 2022).
Throughout the health crisis, numerous states, counties, and local governments have

mandated using nonmedical masks, like cloth masks, in public spaces and businesses,
particularly where maintaining physical distance is challenging.
The independent variables appear as follows.
3.4.1 Problem Stream
3.4.1.1 Vulnerable population ratio (65Y+) (Problem Stream)
A substantial proportion of individuals aged 65 and above in a population can significantly
influence mask mandates and other health directives issued by state governments due to the
distinct vulnerability of this age group to infections, including COVID-19. A declined
immune system performance characterizes advancing age, particularly when reaching 65 and
beyond, making the elderly notably susceptible to various viral, bacterial, or otherwise
infections, resulting in heightened risk and potentially severe consequences of disease (Vally,
2020). Not only are the elderly more likely to contract illnesses, but the outcomes, including
prolonged recovery, complications, and, in severe instances, fatality, tend to be more
pronounced for them.
Consequently, when crafting public health policies, especially during global health crises like
the COVID-19 pandemic, policymakers could presumably prioritize safeguarding regions
with a prominent elderly demographic, deploying more vigorous preventive measures. States
or areas with a significant population of elderly individuals might observe the implementation
of stricter COVID-19 preventive actions, potentially including intensified testing procedures,
thorough contact tracing, and perhaps more rigid quarantine or lockdown directives. The
dualfold aim is to protect older people while concurrently mitigating potential burdens on

healthcare systems that might struggle with an influx of severe cases from this demographic.
Therefore, policymakers must remain aware and responsive to these susceptibilities, ensuring
enacted protective measures are thorough and tailored to shield those most at risk.
Hypothesis H3.1.1: A positive correlation exists between the prevalence of a vulnerable
(elderly) population and state governments' enforcement of stringent COVID-19 policies.
Specifically, as the percentage of the population aged 65 and above increases, stricter
COVIDrelated health mandates, such as mask-wearing, will be more likely to be
implemented and enforced.
3.4.1.2 Hospital beds per 1000 population (Problem Stream)
The availability of hospital beds per 1000 population can significantly influence mask
mandates and other health-related policies implemented by state governments, especially
during health crises like the COVID-19 pandemic. In scenarios where hospitals experience a
scarcity of beds amid surges in COVID-19 cases, the resulting strain on healthcare
infrastructures becomes substantial. This limited capacity not only impedes the ability of
hospitals to serve individuals affected by the virus adequately but also impacts their capability
to attend to other patients with pressing health requirements. Consequently, such
circumstances might jeopardize patient outcomes, escalate mortality rates, and place
additional burdens on healthcare professionals.
Given these challenges, it is reasonable to anticipate that government entities might institute
rigorous health directives to curtail virus dissemination. These directives could involve
advanced diagnostic testing and comprehensive contact tracing to identify and isolate affected

individuals promptly. Stricter quarantine measures, accompanied by meticulous supervision
and compliance, might be emphasized. Additional preventive approaches could include
advocating for enhanced physical distancing, imposing restrictions on sizable gatherings,
implementing bans, and potentially enforcing temporary shutdowns of non-essential
businesses, along with restricting travel to prevent the virus from spreading across locales.
Hypothesis H3.1.2: A negative relationship exists between the availability of hospital beds per
1000 population and the implementation of strict governmental health policies. Specifically,
as the number of available hospital beds decreases amidst a surge in COVID-19 patients,
governments are likely to adopt and enforce more stringent health measures, including mask
mandates, to manage and potentially reduce the number of COVID-19 cases.
3.4.1.3 Proportion of private insurance (Employer + Non-Group) (Problem Stream)
The proportion of individuals participating in private insurance programs, through
employerprovided plans and non-group policies, can influence the mask mandates enacted by
state governments. Individuals with private insurance often have access to superior healthcare
resources and services, including high-quality masks and potentially prioritized access to
vaccinations. This may inadvertently foster a sense of security and diminished perceived
vulnerability amidst a health crisis like the COVID-19 pandemic. Moreover, their
comprehensively designed health plans, bolstered by a holistic health strategy, and
partnerships with medical experts to offer wellness guidance, may subtly shift the policy-
making impetus. States with a higher proportion of privately-insured individuals might

witness a nuanced policy dynamic, where the perceived widespread access to quality
healthcare resources and diminished severity perception of the health crisis might render
policymakers more amenable to instituting lenient or selective mask mandates.
In this context, the perceived sufficient safeguarding against COVID-19 among privately
insured populations might influence state-level considerations about the stringency and
comprehensiveness of mask mandates, potentially adjusting them to be more accommodating
or targeted, as compared to states with lower proportions of privately-insured individuals,
where mask mandates might be perceived as more vital and consequently, be more stringent.
Hypothesis 3.1.3: The higher the proportion of individuals covered by private insurance
within a state, the more lenient or selectively-applied the government's mask mandates will
be, due to the potentially diminished perceived severity and urgency of implementing
restrictive policies among the privately-insured populace.
3.4.1.4 Impact of Monthly Added COVID Cases per 100,000 Population on Mask Mandates
(Problem Stream)
Assessing the impacts of the number of new COVID-19 cases per 100,000 population each
month on mask mandate policies enacted by state governments requires a nuanced
understanding of the virus's temporal and immediate transmission risk. The new cases per
100,000 population every month serve as a potent, dynamic indicator of the current state of
the epidemic, reflecting not only the present burden on healthcare systems but also providing
a more immediate gauge of transmission risk and epidemiological activity within the state.

An increase in COVID cases per 100,000 population each month might indicate an elevated
risk of transmission, urging the state governments to revisit, recalibrate, and potentially
tighten mask mandates to mitigate further spread. Furthermore, such an upswing may
underscore an urgent need to reinforce preventive measures, with a potential implication
being that existing policies (e.g., mask mandates) might be insufficient or inadequately
enforced. Consequently, an increasing monthly caseload per capita could not only shape the
stringency of mask mandates. However, it might also inform the enforcement and public
compliance strategies, involving various sectors to enact multi-faceted, coherent responses.
During the latter part of 2020, with states grappling with escalating COVID-19 infections and
resultant pressures on healthcare systems, divergent strategies were employed to navigate the
crisis, often reflective of the immediate case trajectory. Whereas high-density areas,
particularly those witnessing spikes in new cases, adopted stringent containment measures
like rigorous lockdowns and amplified testing, states also engaged in continuous adjustments
to policies like mask mandates, which were tethered to real-time and predictive
epidemiological data. Sustained efforts in contact tracing, public communication on safety
protocols, and partnerships with healthcare entities were instrumental in formulating adaptive,
situationally pertinent responses, showcasing the necessity of aligning policy adjustments,
including mask mandates, with the dynamic, real-time progression of the pandemic.
Hypothesis 3.1.4: As the monthly rate of new COVID-19 cases per 100,000 population
escalates within a state, authorities are likely to implement and intensify mask mandates. This
strategy serves as a direct countermeasure to manage the surge in transmission risks, aiming

to reduce the spread of the virus, protect vulnerable populations, and ensure that healthcare
systems remain capable of addressing the increased demand without being overwhelmed by a
sudden influx of patients.
3.4.1.5 Impact of Interstate Travel Restrictions on Mask Mandates
The diversity of interstate travel restrictions during the COVID-19 pandemic, enacted by
various state governments across the United States, potentially impacted the implementation
and enforcement of mask mandates in numerous ways. States that initiated rigid travel
restrictions, particularly those imposing mandatory quarantine measures and health
screenings at prominent transit points, often faced intertwining challenges and considerations
related to mask mandates. For instance, areas enforcing stringent travel rules may also align
with implementing rigorous mask mandates to prioritize public health and safety consistently.
Contrarily, states that adopted a lax approach to travel limitations occasionally paralleled this
stance in their mask mandate, or lack thereof, reflecting a broader, potentially
economicallymotivated, strategy to ease restrictions.
In light of varying infection rates and demographic susceptibilities, state governments tailored
their travel and mask policies in response to internal COVID-19 dynamics and by considering
the epidemiological contexts of neighboring states and potential inbound travel hotspots.
Therefore, the interplay between travel restrictions and mask mandates emerges as a critical
facet of public health policymaking during the pandemic, with states negotiating between
safeguarding public health, facilitating economic recovery, and navigating public and political
opinion.

These policies experienced continuous evolution, adapting to the vicissitudes of the
pandemic’s progression within individual states and the overarching situation in the United
States, underpinned by emergent scientific knowledge and varying pressures from different
sectors.
Hypothesis 3.1.5: The stringent nature of interstate travel restrictions enacted by state
governments is positively correlated with the strictness of mask mandates, as states
employing rigorous travel limitations might be more inclined to adopt and enforce stringent
mask mandates to mitigate the spread of COVID-19 and protect vulnerable populations.
Conversely, states adopting a more lenient approach towards interstate travel might
demonstrate a parallel leniency in their mask-wearing mandates and enforcement, potentially
prioritizing economic and social considerations over adopting strict public health
interventions. Various factors might influence this relationship, including political ideology,
public opinion, financial health, and the prevailing COVID-19 case numbers in a particular
state.
3.4.2 Policy Stream
3.4.2.1 Impact of Changes in Total Medicaid and CHIP Enrollment on Mask Mandates
Examining the fluctuation in total Medicaid and CHIP enrollment in each state can offer
valuable insights into the state's approach to health policy, precisely its response to the
COVID19 pandemic and the implementation of mask mandates. Utilizing the multiple
streams framework, which encompasses a range of strategies and ideas available to

policymakers, I can connect Medicaid enrollment changes to the broader context of public
health policies.
Total Medicaid and CHIP enrollment can indicate a state's effort for the health and well-being
of its low-income citizens. It goes beyond the mere allocation of funds and reflects the state's
overarching policy direction in addressing the needs of vulnerable communities. While other
metrics may provide information on health policy coverage and the strictness of travel
restrictions, Medicaid enrollment is a more immediate gauge of policy implementation. The
extent to which a state allocates resources to Medicaid can signal its broader health policy
goals, positioning it within the policy stream defined by the multiple streams framework.
Hypothesis 3.2.1: If a state's healthcare system can efficiently manage and handle the influx
of COVID-19 cases, and if increased Medicaid expenditure is correlated with improved
pandemic control, the state government may be more inclined to consider easing state-level
travel restrictions. This presumption assumes that the state can effectively mitigate the
potential risks of increased travel-related COVID-19 cases.
3.4.2.2 Impact of Total Full Vaccination Rate on Mask Mandates
The total full vaccination rate within states plays a pivotal role in shaping COVID-19
response policies across America. Throughout 2020 and 2021, the development and
distribution of vaccines emerged as a central focus of pandemic management. The U.S. Food
and Drug Administration (FDA) granted emergency use authorizations for several vaccines,
commencing with the Pfizer-BioNTech vaccine in December 2020, followed by Moderna and
Johnson & Johnson (Pfizer, 2021). Higher vaccination rates can trigger the relaxation or

removal of specific COVID-19 restrictions. As vaccinated individuals increase, the risk of
severe illness, hospitalization, and death significantly diminishes. This risk reduction
empowers policymakers to contemplate easing mask mandates, social distancing
requirements, capacity limitations, and travel restrictions. Vaccination rates serve as a critical
indicator of reduced transmission risk and offer guidance for decisions regarding the
reopening of economic sectors and the return to more typical social activities.
Analyzing data over a sufficient timeframe is imperative for conducting a meaningful and
accurate comparison of state vaccination rates. The initial weeks or months following the
vaccine rollout may only provide insights into the early distribution efforts, rather than
indicative of long-term patterns. To ensure consistency in statistical timing and align the
vaccination rate with other relevant variables, this study compares data from January 12 to
June 30, 2021. This period represents the time frame after the initial vaccine release, enabling
the evaluation of vaccination rates among different states based on available data during that
period.
Hypothesis 3.2.2: As the total full vaccination rate within a state increases, the state
government is more likely to relax stringent COVID-19 policies, including mask mandates.
This hypothesis is based on the premise that higher vaccination rates are associated with a
reduced risk of severe illness and transmission, thus allowing policymakers to consider easing
public health
restrictions.
3.4.3 Politics Stream

3.4.3.1 Political Affiliation on Mask Mandates
Mete (2002) suggests that the political affiliation of a state, whether Democratic or
Republican, can significantly impact the enforcement of mask mandates. This observation
matches the prevailing belief that Democratic officials endorse stricter regulations, while
Republicans often suggest limited government intervention (Teske 2004).
On a broader scale, the approach advocated by President Biden encompassed a
comprehensive nationwide emergency response aimed at protecting lives, ensuring the safety
of frontline workers, and mitigating the spread of COVID-19. His plan emphasized removing
financial barriers associated with COVID-19 prevention and healthcare access. Furthermore,
he proposed substantial economic interventions to support workers, families, and small
businesses adversely affected by the pandemic, to strengthen the American economy during
these challenging times (Kates et al., 2020).
Hypothesis 3.3.1: States with more Biden voters in the 2020 presidential election are inclined
to implement and maintain stricter COVID-19 policies, including mask mandates. This
hypothesis is based on the premise that Democratic-leaning states, which demonstrated
support for President Biden in the recent election, are potentially more inclined to adopt and
enforce stringent measures aimed at reducing the spread of COVID-19. This tendency may
stem from their broader pro-regulation stance, reflecting a political ideology that favors more
active governmental intervention in public health crises to ensure safety and compliance
among the population.

3.5 Research Methods and Measurement
3.5.1 Dependent Variable and Logistic Regression Analysis
This study aims to discern the multifaceted influences that various factors exert on the
stringency of mask mandates and their temporal evolution during the COVID-19 pandemic.
This study employs a logit analysis to explore the relationships between the variables above.
The analysis utilizes data from August 1, 2020, to January 31, 2022. This study conducts a
cross-sectional analysis to investigate the determinants of mask mandate strictness
implemented by the 50 states of the United States. The dependent variable represents the
temporal evolution of mask mandates within each state. In this research context, the
dependent variable is specifically coded to reflect public health policy changes regarding
mask mandates: a value of 2 denotes the initiation of mask mandates, 1 indicates exemptions
for fully vaccinated individuals, and 0 signifies the termination of mask mandates. This
variable is measured on a monthly basis, allowing researchers to observe and analyze any
shifts in policy that occur over time, thus capturing the dynamic nature of public health
responses during the pandemic.
3.5.2 Independent Variables
The analysis encompasses several independent variables, each contributing to a deeper
understanding of the dynamics surrounding mask mandates and travel restrictions during the
COVID-19 pandemic. These variables are critical in evaluating how different regions respond
to health crises. They include political affiliation of the state leadership, population density,
public health infrastructure, rates of COVID-19 infection, and public compliance levels. Each

factor plays a significant role in shaping local responses to the pandemic and the
implementation of preventative measures. These variables include:
(1) Vulnerable Population Ratio (Aged 65+): Represented as a percentage of the total state
population, measured annually.
(2) Hospital Beds per 1,000 Population: Quantified annually.
(3) Proportion of Private Insurance (Employer + Non-Group): Assessed annually.
(4) Monthly Added COVID Cases per 100,000 Population: Recorded monthly.
(5) Changes in Total Medicaid and CHIP Enrollment: Categorized as 1, 2, 3, 4, and 5 to
indicate varying degrees of change on a state-by-state basis.
(6) Full Vaccination Rates: Measured every month.
(7) Political Affiliation of Each State: Categorized as either '1' for states governed by
Democrats or '0' for states governed by Republicans, assessed annually.
(8) Travel Restriction Days: Counted every month.
3.5.3 Phased Analysis
The cross-sectional analysis is conducted in three distinct phases based on the availability of
data:
Phase 1 (August 2020 to January 2021): The last half-year of the Trump administration was
marked by evolving COVID-19 dynamics.
Phase 2 (February 2021 to July 2021): The initial months of the Biden administration
coincided with the rollout of COVID-19 vaccines and declining case counts.
Phase 3 (August 2021 to January 2022): A period characterized by a resurgence of COVID-19
cases.
3.5.4 Data Sources
Data for this research is meticulously sourced from reputable databases and websites are
shown in Table 3.1.,including Ballotpedia, Population Reference Bureau, Becker’s Hospital
Review, Kaiser Family Foundation (KFF), worldometer, Medicaid Gov., and Our world in
data.
3.5.5 Sampling Frame
In this study, a thorough and inclusive approach has been implemented, encompassing the
entire population across all 50 states of the United States. This comprehensive scope ensures
an exhaustive examination of the intricate relationships among the selected variables, thereby
providing a rich, nuanced understanding of the dynamics at play. By integrating data from
such a wide and diverse geographic area, the research offers deep, valuable insights that are
essential for making informed decisions.
Table 3.1: Data Sources
Data name Source of data Data type
Mask mandate Ballotpedia Monthly data
Travel restriction days Ballotpedia Monthly data
65 years old and over Population Reference
Bureau
Yearly data
Population by each state Ballotpedia Yearly data
Hospital beds per 1k population Becker’s Hospital Review Yearly data
Proportion of private insurance Kaiser Family Foundation Yearly data
COVID Cases per 100,000
Population
worldometer Monthly data
total medicaid+CHIP enrollment Medicaid Gov. Yearly data
The total full vaccination rate Our world in data Monthly data
Political affiliation 270 to Win Yearly data
3.6 Results
3.6.1 The Impact of Various Factors on State Government Mask Mandates (Aug. 2020 – Jan.
2021)
The primary dependent variable in this study was "maskmandate", a term specifically coined
to represent the nature and extent of the mask mandates implemented by state authorities.
This variable was quantitatively assessed to determine the level of strictness in each state’s
mandate. The analysis included factors such as the rate of COVID-19 cases and deaths in
each state, political affiliations of the state governments, public health policies, and
demographic data such as population density and age distribution.
Vulnerable Population Ratio (plus): With a positive coefficient and a p-value of 0.012, this
variable is statistically significant and supports Hypothesis H3.1.1. It indicates that an
increase in the elderly population percentage is associated with stricter mask mandates.
Hospital Beds Availability (bedsper1000): The negative coefficient is in line with Hypothesis
H3.1.2, and with a p-value of 0.050, it is marginally significant (just on the edge of
conventional significance levels). This suggests that fewer hospital beds per capita might be
associated with stricter mask mandates.

Table 3.2: The Impact of Various Factors on State Government Mask Mandates (August
2020 - January 2021)
Variable Coefficient and Std. Err. P value > |z|
Vulnerable population
ratio
19.600
(7.834)
.012*
Hospital Beds per 1,000
Population
-.468
(0.238)
.050*
Proportion of Private
Insurance
3.242
(2.461)
.188
Monthly Added Cases
per 100k Population
.000
(0.000)
.335
Total Medicaid and
CHIP Enrollment
.031
(0.267)
.907
Political Affiliation of
Each State
1.816
(0.444)
.000***
Travel Restriction Days .019
(0.016)
.227
(Constant)
-3.949
(2.150)
.066
Note. SS = Sum of Squares; df = degrees of freedom; MS = Mean Square; MSE = Mean
Square
Error. Model summary: Number of obs: 300,LR chi2(7) = 67.76, Prob > chi2 = 0.0000, Pseudo
R2 = 0.1876, Log likelihood = -146.76396
* p<0.05, **p<0.01, ***p<0.001
Proportion of Private Insurance (private): The positive coefficient contradicts Hypothesis H
3.1.3, and with a p-value of 0.188, it is not statistically significant.
Monthly Added COVID Cases (newlyaddedper100k): The coefficient is positive but not
statistically significant with a p-value of 0.335, providing no support for Hypothesis H 3.1.4
within this dataset.
Impact of Interstate Travel Restrictions (travelresdays): The coefficient is negative, which is
not consistent with H 3.1.5, and the p-value of 0.227 indicates that this variable is not

statistically significant at conventional levels (e.g., p<0.05), thus not supporting Hypothesis H
3.1.5 within this period.
Impact of Changes in Medicaid and CHIP Enrollment (medicaidchipchange): This variable
has a negative coefficient and is not significant with a p-value of 0.907, which does not
support Hypothesis H 3.2.1 in this context.
Political Affiliation Impact (demrep2020): With a positive coefficient and a p-value of 0.000,
this variable is highly statistically significant and supports Hypothesis H 3.3.1, suggesting
that states with a higher proportion of Democratic voters in the 2020 presidential election
were more likely to have stricter mask mandates.
In summary, the analysis provides strong evidence for Hypotheses H3.1.1 and H 3.3.1,
marginal support for Hypothesis H3.1.2, and no significant evidence for Hypotheses H 3.1.3,
H 3.1.4, and H 3.2.1 with the given dataset and time frame. The model's overall predictive
power is relatively low, with a Pseudo R^2 of 0.1876. This metric suggests that, although
certain variables within the model significantly contribute to the explanation of variations in
the strictness of mask mandates across different jurisdictions, the model does not capture the
full complexity of the factors at play. In essence, this indicates that there are additional
variables and dynamics not accounted for within the current framework that could have a
substantial impact on the formulation and implementation of mask mandates. The relatively
low Pseudo R^2 underscores the need for a more comprehensive model that incorporates a
wider range of predictors. This could include factors such as local public health capacity,
socio-economic disparities, cultural attitudes towards mask-wearing, and the influence of

misinformation, all of which could provide further insights into the multifaceted decision-
making process behind the adoption and enforcement of mask mandates.
3.6.2 The Impact of Various Factors on State Government Mask Mandates (February 2021 -
July 2021)
This study conducted over the period from February 2021 to July 2021, with the primary
objective of identifying and understanding the various factors that influenced the level of
strictness in mask mandates imposed by state governments in the United States. This period
was critical in the ongoing battle against the COVID-19 pandemic, and state responses varied
significantly, prompting a closer examination as presented in Table 3.3.
Vulnerable Population Ratio ("plus"): Despite the positive coefficient, the variable is not
statistically significant with a p-value of 0.867, not supporting Hypothesis H3.1.1 within this
dataset.
Hospital Beds Availability ("bedsper1000"): The coefficient is negative, but with a p-value of
0.250, it does not provide statistically significant evidence for Hypothesis H3.1.2.
Proportion of Private Insurance ("private"): The coefficient is negative, but not statistically
significant with a p-value of 0.355, which does not support Hypothesis H 3.1.3.
Monthly Added COVID Cases ("newlyaddedper100k"): The coefficient is positive, indicating
a directionally correct relationship, but with a p-value of 0.718, it is not statistically
significant, providing no support for Hypothesis H 3.1.4 within this timeframe.

Interstate Travel Restrictions ("travelresdays"): The positive coefficient and a p-value of
0.010 indicate a statistically significant relationship, supporting Hypothesis H 3.1.5. More
travel restriction days are associated with stricter mask mandates.
Table 3.3: The Impact of Various Factors on State Government Mask Mandates
(February 2021 - July 2021)
Variable Coefficient and Std. Err. P value > |z|
Vulnerable
population ratio
1.571
(0.018)
.867
Hospital Beds per
1,000 Population
-.400
(0.347)
.250
Proportion of
Private Insurance
-5.888
(3.071)
.055
Monthly Added
Cases per 100k
Population
.000
(.000)
.718
Total Medicaid and
CHIP Enrollment
-.278
(0.291)
.339
Political Affiliation
of Each State
.694
(.114)
0.000***
Full Vaccination
Rates
7.443
(1.389)
0.000***
Travel
Restriction
Days
.047
(.018)
0.010*
(Constant)
.276
(.679)
.001
Note. N = 300. Model summary: LR chi2(8) = 154.71, Prob > chi2 = 0.0000, Pseudo R2 =
0.3755, Log likelihood = -128.66063 *
p<0.05, **p<0.01, ***p<0.001
Changes in Medicaid and CHIP Enrollment ("medicaidchipchange"): The positive coefficient
is statistically significant with a p-value of 0.039, indicating that an increase in Medicaid and
CHIP enrollment is associated with stricter mask mandates, which contrasts with the expected
direction in Hypothesis H 3.2.1. Total Full Vaccination Rate ("vaccinationrate"): Consistent

with Hypothesis H3.2.2, the negative coefficient is highly significant with a p-value of 0.000,
suggesting that higher vaccination rates are associated with less strict mask mandates.
Political Affiliation ("demrep2020"): The positive and highly statistically significant
coefficient (pvalue of 0.000) supports Hypothesis H 3.3.1, showing that states with more
Democratic voters tend to have stricter mask mandates.
Overall, for the period of February 2021 to July 2021, the model suggests that the travel
restriction days and political affiliation are significantly associated with the strictness of mask
mandates. The model's predictive power has improved, with a Pseudo R2 of 0.3755,
indicating a better fit compared to the previous model. Notably, the vaccination rate emerged
as a strong predictor, suggesting that as vaccination rates increase, the strictness of mask
mandates decreases. This factor provides a new dimension to the policy dynamics during the
Biden administration's first half-year in office.
3.6.3 The Impact of Various Factors on State Government Mask Mandates (August 2021 -
January 2022)
This part covers the period from August 2021 to January 2022, detailed in Table 3.4, a
meticulous examination was undertaken to understand the dynamics influencing the strictness
of mask mandates enacted by state governments across the United States. This timeframe was
particularly crucial as it marked a significant phase in the ongoing COVID-19 pandemic, with
varying responses from state authorities.
Vulnerable Population Ratio (over 65 Years old) ("plus"): The negative coefficient and a
pvalue of 0.023 suggest a statistically significant relationship, but the direction is opposite to

that predicted by Hypothesis H3.1.1, indicating that a higher percentage of the elderly
population is associated with less strict mask mandates in this period.
Hospital Beds Per 1000 Population ("bedsper1000"): The negative coefficient is statistically
significant (p-value of 0.005), supporting Hypothesis H3.1.2, suggesting that fewer hospital
beds per capita are associated with stricter mask mandates.
Proportion of Private Insurance ("private"): The coefficient is negative and statistically
significant (p-value of 0.007), suggesting that a higher proportion of private insurance
coverage is associated with stricter mask mandates, which is counter to Hypothesis H 3.1.3.
Table 3.4: The Impact of Various Factors on State Government Mask Mandates (August
2021 - January 2022)
Variable Coefficient and Std. Err. P value
Vulnerable
population ratio
-3.867
(2.162)
2.162
Hospital Beds per
1,000 Population
-1.052
(0.737)
0.737
Proportion of
Private Insurance
-2.448
(.713)
0.713
Monthly Added
Cases per 100k
Population
.000
(.000) 0.000***
Total Medicaid and
CHIP Enrollment
-.155
(0.066)
0.066
Political Affiliation
of Each State
.649
(.114)
0.114
Full Vaccination
Rates
-.247
(.567)
0.567
Travel
Restriction
Days
.206
(.060)
0.060
(Constant)
2.950
(.607)
0.607

Note. N = 300. Model summary: LR chi2(8)=132.95, Prob > chi2 = 0.0000, Pseudo R2 =
0.4603,
Log likelihood = -77.931601
* p<0.05, **p<0.01, ***p<0.001
Monthly Added COVID Cases Per 100,000 Population ("newlyaddedper100k"): The positive
coefficient is not statistically significant (p-value of 0.362), providing no support for
Hypothesis H 3.1.4 within this timeframe.
Impact of Interstate Travel Restrictions on Mask Mandates ("travelresdays"): With a negative
coefficient and a p-value of 0.019, this variable is statistically significant and suggests that
more travel restriction days are associated with less stringent mask mandates, contrary to
Hypothesis 3.1.5.
Changes in Total Medicaid and CHIP Enrollment ("medicaidchipchange"): The positive and
significant coefficient (p-value of 0.007) indicates that an increase in Medicaid and CHIP
enrollment is associated with stricter mask mandates, aligning with Hypothesis H 3.2.1.
Total Full Vaccination Rate ("vaccinationrate"): The coefficient is negative but not
statistically significant (p-value of 0.567), indicating no significant association with the
strictness of mask mandates for this period.
Political Affiliation on Mask Mandates ("demrep2021"): The positive and highly statistically
significant coefficient (p-value of 0.000) strongly supports Hypothesis H 3.3.1, showing that
states with more Democratic voters tend to have stricter mask mandates.5.4 The Impact of
Various Factors on State Government Mask Mandates (February 2021 - January 2022).

In summary, for the period of August 2021 to January 2022, the logistic regression analysis
found statistically significant relationships for travel restrictions, elderly population
percentage, hospital beds per 1,000, private insurance coverage, Medicaid and CHIP
enrollment changes, and political affiliation with the strictness of mask mandates. However,
some relationships were in the opposite direction than hypothesized. The variable for the
monthly rate of new
COVID-19 cases per 100,000 and the vaccination rate did not show significant associations.
The Pseudo R2 value of 0.4603 indicates a moderate explanatory power of the model,
suggesting that it reasonably predicts the dependent variable, which in this case is the
strictness of mask mandates. This highlights the model's effectiveness in capturing key
factors.
3.6.4 The Impact of Various Factors on State Government Mask Mandates (August 2020 -
January 2022)
Table 3.5 shows the logistic regression results for the entire period from August 2020 to
January
2022, without considering the complete vaccination rate, can be interpreted as follows:
Table 3.5: The Impact of Various Factors on State Government Mask Mandates (August
2020 - January 2022)
Variable Coefficient and Std. Err. P value
Vulnerable
population ratio
2.596
(1.276)
.055
Hospital Beds per
1,000 Population
-.479
(.160)
.003**
Proportion of
Private Insurance
-1.667
(1.404)
.235
Monthly Added
Cases per 100k
.000
(.000)
.043*
Population
Total Medicaid and
CHIP Enrollment
-.075
(0.135)
.576
Political Affiliation
of Each State
1.042
(.202)
.000***
Travel
Restriction
Days
.056
(.009)
.000***
(Constant)
.840
(1.209)
0.483
Note. N = 900. Model summary: LR chi2(7) = 190.27, Prob > Chi2 = 0.0000, Pesudo R2 =
0.1538, Log Likelihood = -523.56657 *
p<0.05, **p<0.01, ***p<0.001
Travel Restrictions (travelresdays): The positive coefficient is highly significant (p-value of
0.000), indicating that an increase in travel restriction days is strongly associated with stricter
mask mandates, supporting Hypothesis 3.1.5.
Percentage of 65+ Population (plus): The coefficient is positive but not statistically significant
(p-value of 0.539), providing no support for Hypothesis H3.1.1 in this analysis.
Hospital Beds per 1,000 Population (bedsper1000): The negative coefficient is significant
(pvalue of 0.003), which supports Hypothesis H3.1.2, suggesting that a lower availability of
hospital beds is associated with stricter mask mandates.
Proportion of Private Insurance (private): The negative coefficient is not statistically
significant (p-value of 0.235), offering no evidence in support of Hypothesis H 3.1.3.
COVID Cases per 100,000 Population (newlyaddedper100k): The negative coefficient is
significant (p-value of 0.043), contrary to Hypothesis H 3.1.4, suggesting that an increase in
COVID-19 cases per 100,000 is associated with less strict mask mandates in this dataset.

Total Medicaid + CHIP Enrollment Change (medicaidchipchange): The coefficient is negative
but not statistically significant (p-value of 0.576), providing no support for Hypothesis H
3.2.1.
Political Affiliation (demrep2020/2021): The positive coefficient is highly significant (p-value
of 0.000), supporting Hypothesis H 3.3.1, which posits that states with more voters for Biden
would have stricter mask mandates.
In this model, significant variables associated with the strictness of mask mandates include
travel restrictions, hospital beds availability, and political affiliation, with the latter two
variables showing associations that align with the proposed hypotheses. However, the
presence of a vulnerable population and changes in Medicaid and CHIP enrollment did not
have a statistically significant association with mask mandate strictness in this analysis. The
pseudoR-squared value of 0.1538 indicates that while the model possesses some explanatory
power, it accounts for approximately 15% of the variance in the outcome. This observation
suggests that there are additional factors not captured in the current model that significantly
influence the outcome. It highlights the necessity for further model refinement and more
comprehensive investigation to include these variables, thereby enhancing the model’s
accuracy and reliability in predicting outcomes more effectively.
3.6.5 The Impact of Various Factors on State Government Mask Mandates (February 2021 -
January 2022)
The logistic regression analysis for February 2021 to January 2022, reflecting the first year of
the Biden administration and including vaccination rates, shows the following:

Travel Restrictions (travelresdays): A positive coefficient with a p-value of 0.000 suggests
that an increase in travel restriction days is significantly associated with stricter mask
mandates, supporting Hypothesis 3.1.5.
Percentage of 65+ Population (plus): The negative coefficient, not statistically significant
with a p-value of 0.290, does not support Hypothesis H3.1.1.
Hospital Beds per 1,000 Population (bedsper1000): A negative coefficient with a p-value of
0.004 indicates a significant association, supporting Hypothesis H3.1.2; fewer hospital beds
are associated with stricter mask mandates.
Proportion of Private Insurance (private): A negative and significant coefficient (p-value of
0.000) indicates that a higher proportion of private insurance coverage is associated with
stricter mask mandates, which is counter to Hypothesis H 3.1.3. COVID Cases per 100,000
Population (newlyaddedper100k): A negative coefficient with a p-value of 0.051 is
marginally significant and suggests that an increase in the monthly rate of new COVID-19
cases per 100,000 population is associated with less strict mask mandates, contradicting
Hypothesis H
3.1.4. Total Medicaid + CHIP Enrollment Change (medicaidchipchange): The coefficient is
negative but not statistically significant (p-value of 0.576), providing no support for
Hypothesis H 3.2.1. Vaccination Rate (vaccinationrate): A highly significant negative
coefficient (p-value of 0.000) supports Hypothesis H 3.2.2, suggesting that higher vaccination
rates are associated with less strict mask mandates.

Table 3.6: The Impact of Various Factors on State Government Mask Mandates
(February 2021 - January 2022)
Variable Coefficient and Std. Err. P value
Vulnerable
population ratio
-7.560
(7.152) 0.290
Hospital Beds per
1,000 Population
-.888
(0.311)
0.004**
Proportion of
Private Insurance
-8.906
(2.432)
0.000***
Monthly Added
Cases per 100k
Population
.000
(.000) 0.051
Total Medicaid and
CHIP Enrollment
-.820
(0.206)
0.000***
Political Affiliation
of Each State
2.946
(0.399)
0.000***
Full Vaccination
Rates
-6.544
(0.730)
0.000***
Travel
Restriction
Days
.066
(.017)
0.000***
(Constant)
11.043
(2.144)
0.000
Note. N = 600. Model summary: LR chi2(7) = 304.47, Prob > Chi2 = 0.0000, Pesudo R2 =
0.4072, Log Likelihood = -221.58911 *
p<0.05, **p<0.01, ***p<0.001
Political Affiliation (demrep2021): A significant positive coefficient (p-value of 0.000)
strongly supports Hypothesis H 3.3.1; states with more Democratic voters tend to have
stricter mask mandates.
In this model, significant predictors of mask mandate strictness include travel restrictions,
hospital beds per 1,000 population, private insurance coverage, vaccination rates, and
political affiliation. The results show that the presence of a vulnerable elderly population does
not significantly affect mask mandate strictness in this period. Notably, higher vaccination

rates are significantly associated with less strict mask mandates. The Pseudo R-squared value
of 0.4072 suggests that the model has moderate explanatory power for the strictness of mask
mandates during this period.
3.6.6 Correlation Analysis of Independent Variables Related to Mask Mandate Strictness
(August 2020 - January 2022)
The correlation table provided reflects the relationships between each of the independent
variables (IVs) for the period from August 2020 to January 2022. Notably:
There is a strong negative correlation between the number of hospital beds per 1,000
population (bedsper1000) and the percentage of the population aged 65 and over (plus), with
a correlation coefficient of -0.9960 (p=0.0040), suggesting that a trend where states with a
higher proportion of elderly residents, a demographic known to require more medical
services, surprisingly tend to have fewer hospital beds available per capita. This discrepancy
highlights a potential area of concern in healthcare resource allocation, indicating a possible
mismatch between the population's needs and the availability of essential healthcare
infrastructure.
The analysis reveals a notable negative correlation between the number of travel restriction
days each month (travelresdays) and the number of hospital beds per 1,000 population
(bedsper1000), with a correlation coefficient of -0.1397 and a highly significant p-value of
0.0000. This suggests that states imposing more travel restrictions tend to have fewer hospital
beds per capita. The finding indicates a potential inverse relationship between public health
policy measures and healthcare resource allocation, warranting deeper exploration to
understand the underlying causes and implications of this trend.

Table 3.7: The Correlation between each IV (August 2020 - January 2022)
Travel
restrictio
ns days
Vulnerab
le
populatio
n ratio
Hospit
al beds
per 1k
Proportio
n of
private
insuranc
e
Monthl
y
added
cases
per
100k
Total
Medicai
d and
CHIP
Political
affiliatio
n each
state
of
Travel
restrictio
ns days
1.0000
Vulnerabl
e
populatio
n ratio
0.1737
0.0000
1.0000
Hospital
beds per
1k
-0.1397
0.0000
0.0960
0.0040
1.0000
Proportio
n of
private
insurance
-0.0110
0.7408
-0.2055
0.0000
0.0143
0.6686
1.0000
Monthly
added
cases per
100k
-0.0612
0.0665
-0.0512
0.1244
0.1207
0.0003
-0.0322
0.3340
1.0000
Total
Medicaid
and CHIP
-0.0988
0.0030
-0.0277
0.4971
-0.0198
0.5533
0.1716
0.0000
-0.1535
0.0000
1.0000
Political
affiliation
of each
state
0.2437
0.0000
0.1620
0.0000
-0.6089
0.0000
0.1518
0.0000
-0.1393
0.0000
-0.0220
0.5106
1.0000
Political affiliation (demrep2020/2021) is positively correlated with travel restriction days
(travelresdays) with a coefficient of 0.2437 (p=0.0000), suggesting that states with a higher
proportion of Democratic voters tend to implement more travel restrictions.
There is a substantial negative correlation between Medicaid and CHIP enrollment change
(medicaidchipchange) and travel restriction days (travelresdays), with a coefficient of -0.9898

(p=0.0030). This indicates that states with higher increases in Medicaid and CHIP enrollment
have fewer travel restriction days.
A strong positive correlation exists between political affiliation (demrep2020/2021) and the
percentage of the population aged 65 and over (plus), with a correlation coefficient of 0.1620
(p=0.0000), suggesting that states with more Democratic voters tend to have a higher
percentage of elderly population.
3.6.7 Correlation Analysis of Independent Variables Related to Mask Mandate Strictness
(February 2021 - January 2022)
The correlation table for the specified period of February 2021 to January 2022 analyzes the
interrelationships among various independent variables (IVs) involved in studying mask
mandate policies. Notable observations from the correlation matrix include:
A moderate positive correlation between political affiliation (demrep2020/2021) and the
percentage of the population aged 65 and over (plus), with a correlation coefficient of 0.1975
(p<0.0000), suggests that states with more Democratic voters tend to have a higher
percentage of elderly population.
A notable negative correlation is observed between the number of hospital beds per 1,000
population (bedsper1000) and political affiliation (demrep2020/2021), with a coefficient of
0.6168 (p=0.0002). This indicates that states with more Democratic voters tend to have fewer
hospital beds per capita.
The total full vaccination rate (vaccinationrate) is negatively correlated with travel restriction
days (travelresdays) with a coefficient of -0.1577 (p=0.0001), suggesting that states with
higher vaccination rates may have fewer travel restrictions.

Table 3.8: The Correlation between each IV (February 2021 - January 2022)
Trave
l
restri
ctions
Vulner
able
popula
tion
Hospit
al beds
per 1k
Private
insura
nce
Monthl
y
added
cases
Medicai
d and
CHIP
Full
vaccina
tion
Politi
cal
affilia
tion
Travel
restricti
ons
1.000
Vulnera
ble
populati
on
0.159
0.000
1.000
Hospital
beds per
1k
-0.085
0.037
0.081
0.047
1.000
Private
insuranc
e
0.071
0.084
-0.233
0.000
0.039
0.337
1.000
Monthly
added
cases
-0.010
0.814
0.007
0.874
0.043
0.288
-0.076
0.063
1.000
Medicai
d &
CHIP
-0.086
0.035
-0.024
0.557
-0.020
0.624
0.167
0.000
-0.099
0.015
1.000
Full
vaccinat
ion
-0.158
0.000
0.045
0.273
-0.132
0.001
0.030
0.469
0.038
0.359
-0.102
0.012
1.000
Political
affiliatio
n
0.181
0.000
0.198
0.000
-0.617
0.000
0.151
0.000
-0.071
0.084
-0.020
0.634
0.180
0.000
1.000
The relationship between the proportion of private insurance (private) and the percentage of
the elderly population (plus) is negatively correlated, with a coefficient of -0.2325
(p<0.0000), indicating that states with a larger elderly population tend to have a lower
proportion of private insurance coverage.
Additionally, a slight negative correlation is observed between the number of COVID Cases
per 100,000 Population each month (newlyaddedper100k) and travel restriction days

(travelresdays), with a coefficient of -0.0906 (p=0.8136), although this is not statistically
significant.
3.7 Discussions
3.7.1 Discrepancies between Hypotheses and Results in the phase from Aug. 2020 to Jan.
2021
The observed discrepancies between the hypotheses and the empirical results can be
attributed to various real-world factors, complexities in data interpretation, and the intricate
dynamics of the COVID-19 pandemic response across different states. An exploration of the
potential reasons for these discrepancies reveals insights into the multifaceted nature of public
health policy implementation:
Proportion of Private Insurance (Contradicts Hypothesis H 3.1.3): The initial hypothesis
posited that states with a higher proportion of individuals covered by private insurance would
implement more lenient mask mandates under the assumption that privately insured
populations might perceive the severity and urgency of the pandemic differently. Contrary to
this hypothesis, the analysis found a positive coefficient, indicating that states with higher
private insurance coverage rates might enforce stricter mask mandates. This could suggest
that access to better healthcare information and resources among privately insured individuals
may heighten awareness and responsiveness to health crises, leading to the adoption of
stricter health measures. Furthermore, demographic or political characteristics associated with

higher private insurance coverage may align with preferences for more proactive health
interventions.
Monthly Added COVID Cases (No Support for Hypothesis H 3.1.4): Despite the intuitive link
between rising COVID-19 case rates and the tightening of mask mandates, this relationship
was not statistically significant in the analysis. This may reflect the myriad factors
influencing state-level decision-making beyond immediate case counts, including economic
considerations, public opinion, and the effectiveness of other mitigation strategies.
Additionally, potential delays between surges in case numbers and the enactment of policy
measures might not have been captured within the study's timeframe, possibly obscuring the
direct impact of rising case rates on policy stringency.
Impact of Interstate Travel Restrictions (Contradicts Hypothesis 3.1.5): The analysis did not
support the hypothesis that stricter interstate travel restrictions would be associated with more
stringent mask mandates. Instead, a negative coefficient was observed, suggesting that states
implementing travel restrictions did not necessarily impose strict mask mandates. This could
indicate a strategic prioritization of travel restrictions as a measure deemed sufficient by some
states to mitigate virus transmission without universal mask mandates. Differences in political
and public receptiveness to travel restrictions versus mask mandates might also play a role,
with travel restrictions potentially viewed as less intrusive in individuals' daily lives.
Impact of Changes in Medicaid and CHIP Enrollment (No Support for Hypothesis H 3.2.1):
The hypothesis that changes in Medicaid and CHIP enrollment would influence mask
mandate policies was not substantiated. The analysis showed a lack of significant correlation,

suggesting that the relationship between healthcare system capacity (as inferred from
Medicaid/CHIP enrollment changes) and mask mandate decisions might not be
straightforward. Instead, public health policy decisions, including mask mandates, may rely
more on immediate health data, political factors, and public sentiment than on broader
healthcare system capacity indicators.
Political Affiliation Impact (Supports Hypothesis H 3.3.1 but Emphasizes Complexity): The
finding that Democratic-leaning states were likelier to implement stricter mask mandates
provides empirical support for the hypothesis linking political affiliation to pandemic
response policies. This underscores the significant influence of political ideologies on public
health measures. However, it also hints at the complexity beyond mere voter preference,
including the roles of state leadership, legislative actions, and local government initiatives,
which could affect how political affiliations translate into policy decisions.
These findings highlight the complexity of public health policy decisions, where a web of
factors, including public opinion, economic impacts, healthcare infrastructure, and political
ideologies, influence causality. The discrepancies between the hypotheses and the results
underscore the need for a nuanced understanding of the multifactorial influences on pandemic
response measures.
3.7.2 Discrepancies between Hypotheses and Results in the phase from Feb. 2021 to Jul. 2021
The analysis of state government mask mandates from February 2021 to July 2021, against
the backdrop of the initial hypotheses, reveals intriguing deviations for several variables.
These discrepancies highlight pandemic policy responses' complex and dynamic nature,

influenced by evolving circumstances and new evidence. The divergences provide insight
into the multifaceted considerations beyond the anticipated factors:
Vulnerable Population Ratio: Contrary to Hypothesis H3.1.1, which posited a direct
correlation between the proportion of elderly and the strictness of mask mandates, the
analysis found this variable to be not statistically significant. This deviation suggests that the
anticipated direct relationship between a vulnerable population's size and policy strings might
have been mitigated by other factors, such as the prioritization of vaccine distribution among
older populations. As vaccines became more accessible, particularly to vulnerable groups, the
urgency to impose strict mask mandates may have decreased, reflecting confidence in
vaccination as a protective measure against COVID-19.
Hospital Beds Availability: The analysis did not find significant support for Hypothesis
H3.1.2, which expected a negative relationship between hospital bed availability and mask
mandate strictness. This outcome might indicate that the healthcare system's capacity, as
represented by hospital bed availability, did not exert as much influence on mask policy
decisions as hypothesized. During this period, the emphasis on vaccination and other
therapeutic advancements could have alleviated concerns over hospital capacity, diminishing
the perceived need to implement stricter mask mandates as a compensatory measure for
healthcare resource limitations.
The proportion of Private Insurance: While not statistically significant, the negative
coefficient for the proportion of private insurance contradicts Hypothesis H3.1.3. This
hypothesis anticipated a more lenient approach to mask mandates in states with higher private

insurance rates. The coefficient's lack of significance and contrary direction suggest that
private insurance coverage might not have played a discernible role in shaping mask mandate
policies. This could reflect a standardized public health approach that prioritizes universal
safety measures over individual insurance status, especially in a public health crisis where the
objective is to protect the entire population.
Monthly Added COVID Cases: Although not statistically significant, the positive direction of
the coefficient for monthly added COVID cases fails to support Hypothesis H3.1.4 as
strongly as expected. This suggests that the increase in COVID-19 cases did not directly
translate into stricter mask mandates within the studied timeframe. The rapid rollout of
vaccinations and the complex dynamics of pandemic management, including public
sentiment and economic considerations, may have influenced the decision-making process,
leading to a nuanced response that did not solely rely on case numbers to dictate mask
mandate strictness.
These variations from the expected hypotheses underscore the nuanced reality of public
health policy-making during a pandemic. They highlight the significant impact of vaccine
distribution, healthcare system resilience, and a holistic approach to public health safety that
goes beyond singular reliance on mask mandates, reflecting a strategic shift in response to the
changing landscape of the COVID-19 pandemic.
3.7.3 Discrepancies between Hypotheses and Results in the phase from Aug. 2021 to Jan.
2022

During the second half-year of President Biden's administration, from August 2021 to January
2022, an analysis was performed to understand the factors influencing the strictness of mask
mandates across the United States. This period was marked by significant developments in
the pandemic's trajectory, including vaccination rollouts and changes in public health policy.
The analysis revealed several deviations from the initial hypotheses, shedding light on the
complex interplay between policy decisions and evolving pandemic conditions.
Vulnerable Population Ratio (Contradicts Hypothesis H3.1.1): Contrary to the expected
positive correlation between the elderly population's prevalence and the enforcement of
stringent COVID-19 policies, the analysis found a statistically significant negative
relationship. This unexpected direction could be attributed to the successful vaccination
campaigns targeting older populations, which might have led states to perceive a reduced
need for strict mask mandates among the most vulnerable groups. Additionally, public health
strategies may have shifted towards relying on vaccination coverage as a primary defense
against COVID-19, thus impacting the approach to mask mandate strictness.
Proportion of Private Insurance (Contradicts Hypothesis H 3.1.3): The finding that a higher
proportion of private insurance coverage is associated with stricter mask mandates contradicts
the hypothesis that privately insured populations would experience more lenient mask
mandates. This reversal could reflect a broader acknowledgment of the pandemic's severity,
pushing states to implement stricter policies irrespective of insurance coverage levels. It may
also indicate that states with higher rates of private insurance, potentially correlating with

better access to healthcare resources, adopted stricter measures as part of a comprehensive
response to protect healthcare systems and populations.
Impact of Interstate Travel Restrictions on Mask Mandates (Contradicts Hypothesis 3.1.5):
The analysis indicated that more travel restriction days are associated with less stringent mask
mandates, contrary to the expectation. This could suggest that states employing travel
restrictions as a primary containment measure might have viewed these restrictions as
sufficient to mitigate virus spread, thus not necessitating stricter mask mandates. It may also
reflect the complexities of balancing economic, social, and public health considerations,
where travel restrictions were deemed a targeted approach to prevent importation of cases,
allowing for more flexibility in local mask policies.
These discrepancies underscore the dynamic nature of public health policy formulation in
response to the evolving pandemic landscape. The variations between expected and observed
outcomes highlight the influence of vaccination progress, changes in virus transmission
dynamics, and the balance between different containment measures. Importantly, these
findings reflect the necessity for adaptable and multifaceted approaches in public health
policy as states navigate the challenges of managing COVID-19 while considering the socio-
economic and healthcare system implications.
3.7.4 Discrepancies between Hypotheses and Results in the phase from Aug. 2020 to Jan.
2022
During the period covering the last half-year of the Trump administration and the first year of
the Biden administration, from August 2020 to January 2022, an extensive analysis was

conducted to assess the factors influencing state government mask mandates in response to
the COVID-19 pandemic. This analysis, encompassing a wide range of variables, found
notable deviations from several hypotheses, shedding light on the complexity of public health
policy decisions in the context of a rapidly evolving health crisis. The discrepancies between
expected outcomes based on the hypotheses and the observed results are analyzed below,
offering insights into potential real-world reasons for these differences.
COVID Cases per 100,000 Population (Contrary to Hypothesis H 3.1.4): Contrary to the
expectation that an increase in COVID-19 cases would correlate with stricter mask mandates,
the analysis found a significant negative association. This unexpected finding might be
attributed to several factors, including possible policy fatigue, increased public resistance to
mandates over time, or a shift in focus towards vaccination as the primary strategy for
managing the pandemic. Additionally, as more data on COVID-19 became available, states
might have adjusted their strategy based on the severity of cases and hospitalization rates
rather than case counts alone, leading to a nuanced approach to implementing mask
mandates.
Percentage of 65+ Population and Proportion of Private Insurance (Lack of Significant
Support): The analysis did not find significant support for Hypotheses H3.1.1 and H 3.1.3,
which anticipated that a higher percentage of vulnerable populations and a higher proportion
of individuals with private insurance would influence the strictness of mask mandates. The
lack of significant findings for these variables could suggest that other factors, such as
vaccination rates among older people and healthcare resource distribution, played more

critical roles in shaping policy decisions during this period. The emergence of vaccines as a
vital tool in the pandemic response likely shifted the focus away from broad non-
pharmaceutical interventions to targeted protection of vulnerable populations and an
emphasis on injection.
Travel Restrictions (Aligned with Hypothesis 3.1.5): The analysis confirmed the hypothesis
that stricter interstate travel restrictions are associated with more stringent mask mandates.
This finding underscores the consistency in states' adoption of comprehensive measures
toward rigorous public health interventions to mitigate the spread of COVID-19. It reflects a
coordinated approach to pandemic management, where travel limitations complemented by
strict mask mandates were seen as integral to controlling the virus's transmission.
Hospital Beds per 1,000 Population (Supports Hypothesis H3.1.2): The observed negative
correlation between hospital bed availability and mask mandate strictness aligns with the
hypothesis, indicating that concerns over healthcare system capacity significantly influenced
policy decisions. This suggests that states with fewer hospital beds per capita, reflecting
potential vulnerabilities in healthcare capacity, were more likely to impose strict mask
mandates as a preventive measure to curb COVID-19 spread and prevent hospital overloads.
Political Affiliation (Supports Hypothesis H 3.3.1): The highly significant positive association
between Democratic voter prevalence and stricter mask mandates corroborates the hypothesis
that political ideology played a crucial role in shaping pandemic responses. This outcome
highlights the impact of political and ideological factors on public health policy, with

Democratic-leaning states more inclined to implement rigorous health measures, including
mask mandates, in line with a more proactive stance on pandemic management.
The analysis over this extended period underscores the intricate balance between public
health priorities, political influences, healthcare system capacities, and societal factors in
shaping the strictness of mask mandates across U.S. states. While some hypotheses were
supported by the data, others were contradicted or lacked significant evidence, illustrating the
complex and multifaceted nature of pandemic policy-making. This complexity highlights the
importance of adapting strategies to changing circumstances and integrating emerging
evidence. The findings demonstrate that effective public health responses require a nuanced
understanding of various dynamics and a flexible approach to policy formulation and
implementation, ensuring that interventions are both timely and contextually relevant.
3.7.5 Discrepancies between Hypotheses and Results in the phase from Feb. 2021 to Jan.
2022
Several findings deviated from the initial hypotheses in the analysis covering the period from
February 2021 to January 2022, which includes significant milestones such as the widespread
availability of COVID-19 vaccines. These deviations provide insights into the evolving
landscape of pandemic response strategies and the complex interplay between public health
measures, healthcare system capacities, and societal behaviors.
COVID Cases per 100,000 Population (Contradicts Hypothesis H 3.1.4): The finding that an
increase in the monthly rate of new COVID-19 cases is associated with less strict mask
mandates contradicts the expectation. Several factors might explain this counterintuitive

result. As vaccination rates increased, the focus of state responses might have shifted from
enforcing strict non-pharmaceutical interventions to promoting vaccination as the primary
means of controlling the pandemic. Additionally, public tolerance for restrictive measures like
mask mandates may have diminished over time, especially in regions with high case rates,
leading to a more nuanced approach that balances public health concerns with socio-
economic considerations and pandemic fatigue.
Proportion of Private Insurance (Contradicts Hypothesis H 3.1.3): The analysis revealed that a
higher proportion of private insurance coverage is associated with stricter mask mandates,
opposite to the hypothesized relationship. This outcome suggests that the assumption linking
private insurance coverage to leniency in mask mandates might have overlooked the
complexities of how healthcare access and insurance coverage influence public health policy
decisions. States with higher levels of private insurance coverage may also have more robust
healthcare systems and possibly greater public health awareness, leading to a proactive stance
in implementing mask mandates as part of a comprehensive pandemic response.
Percentage of 65+ Population (Does Not Support Hypothesis H3.1.1): The lack of a
significant association between the elderly population's percentage and mask mandate
strictness does not support the hypothesis. The widespread rollout of vaccines, mainly
targeting older adults in early phases, likely mitigated the need for strict mask mandates as a
protective measure for vulnerable populations. This reflects a strategic shift towards
vaccination as a critical tool in protecting high-risk groups, reducing reliance on universal
non-pharmaceutical interventions.

Vaccination Rate (Supports Hypothesis H 3.2.2): The highly significant negative association
between vaccination rates and the strictness of mask mandates supports the hypothesis. This
finding underscores the critical role of vaccines in shaping pandemic response strategies. As
vaccination rates increased, providing a direct mechanism to reduce virus transmission and
severe outcomes, the necessity for strict mask mandates decreased, allowing states to adjust
public health measures in line with evolving epidemiological and immunological landscapes.
These deviations and confirmations highlight the dynamic nature of public health
policymaking in response to the pandemic, particularly with the introduction and widespread
distribution of COVID-19 vaccines. The analysis illustrates how vaccine rollout, alongside
other factors like healthcare system capacity and political affiliation, significantly influenced
state-level decisions on mask mandates. It points to the importance of adaptability in public
health strategies to address changing circumstances and the evolving understanding of the
pandemic's challenges.
3.7.6 Overall Findings Based on the Three Phases
3.7.6.1 Consistencies in Both Trump and Biden Eras
The analysis reveals that travel restrictions, across both examined periods, maintain a
consistent and positive association with the implementation of stricter mask mandates. This
finding lends robust support to Hypothesis 3.1.5, reinforcing the notion that policymakers
view both travel restrictions and mask mandates as integral components of a holistic strategy
aimed at curtailing the COVID-19 outbreak. This correlation highlights the necessity of a
steadfast dedication to deploying a variety of public health strategies in tandem to protect

communities from the virus's transmission. It demonstrates the effectiveness of combining
measures such as vaccination, social distancing, and mask-wearing in a comprehensive
approach to mitigate the spread and impact of the virus on populations.
Similarly, the political landscape significantly influenced the rigor of COVID-19 related
policies, particularly mask mandates. The data demonstrates that, during both periods under
review, states characterized by a higher proportion of Democratic voters consistently enacted
stricter mask mandates, affirming Hypothesis H 3.3.1. This trend highlights the enduring
impact of political ideology on public health policy decisions, suggesting that
Democraticleaning states were more inclined to adopt rigorous measures in response to the
pandemic. The persistence of this pattern underscores the critical role that political affiliation
plays in shaping the approach and intensity of state-level responses to a global health crisis. It
highlights how deeply entrenched political ideologies can influence public health strategies
and their implementation, affecting everything from policy decisions to the aggressiveness of
response measures, ultimately impacting public health outcomes significantly.
3.7.6.2 Consistencies in the Trump Era, Discrepancies in the Biden Era
Percentage of 65+ Population (plus): During the Trump administration, data indicated that an
increase in the percentage of the population aged 65 and over (plus) was associated with the
implementation of stricter mask mandates, a finding that aligned with expectations given the
higher vulnerability of older adults to COVID-19. However, this association diminished and
was not statistically significant in the Biden era. This shift is likely attributable to enhanced
vaccination efforts targeted at older populations, which reduced their vulnerability and,

consequently, the perceived need for stringent mask mandates as a primary protective
measure. 3.7.6.3 Discrepancies in the Trump Era, Consistencies in the Biden Era:
Hospital Beds per 1,000 Population (bedsper1000): While the Trump era saw a non-
significant negative association, the Biden era showed a consistent negative association,
indicating that fewer hospital beds were correlated with stricter mask mandates, which
supports Hypothesis H3.1.2. This change might reflect the increasing pressures on healthcare
systems as the pandemic progressed, making hospital capacity a more prominent factor in
policy decisions.
3.7.6.4 Consistencies in the Biden Era
The proportion of Private Insurance (private): Contrary to Hypothesis H 3.1.3, states with
more private insurance coverage had stricter mask mandates during the Biden administration.
This finding suggests that assumptions about the relationship between private insurance
coverage and policy leniency might not account for the complexities of healthcare access and
public health awareness.
COVID Cases per 100,000 Population (newlyaddedper100k): There's a discrepancy with the
expectation (Hypothesis H 3.1.4) that more COVID-19 cases would lead to stricter mask
mandates. The marginal significance and negative coefficient in the Biden era suggest other
factors, such as vaccine distribution and pandemic fatigue, affecting the policy response to
case numbers.

Table 3.9: Overall Comparison Between Expectation from Hypotheses and Actual
Results
Expected Actual
(Aug.
2020-Jan.
2021)
Actual
(Feb.-Jul.
2021)
Actual
(Aug.
2021Jan.
2022)
Actual
(Aug.
2020Jan.
2022)
Actual
(Feb.
2021Jan.
2022)
Travel
restriction days
+ + +* + +*** +***
65 years old and
over
+ +* + - + -
Hospital beds
per 1k
population
- -* - - -** -**
Proportion of
private
insurance
- + - - - -***
Newly Added
COVID Cases
per 100,000
Population
+ + + +*** +* +
total
medicaid+CHIP
enrollment
- + - -* - -***
Total full
vaccination rate
- N/A -*** - N/A -***
Political
affiliation
+ +*** +*** + +*** +***
Note: * p<0.05, **p<0.01, ***p<0.001
Total Medicaid + CHIP Enrollment Change (medicaidchipchange): This variable did not
significantly influence mask mandates, providing no support for Hypothesis H 3.2.1. This
could indicate that changes in Medicaid and CHIP enrollment did not clearly affect -mask
policy strictness.
Vaccination Rate (vaccination rate): The negative association supports Hypothesis H 3.2.2,
with higher vaccination rates linked to less strict mask mandates. This underscores the central

role of vaccinations in public health strategy and the adjustment of mask policies in response
to increased vaccine-induced immunity in the population.
In summary, the regression analysis indicates that certain variables consistently impacted
mask mandate strictness across both the Trump and Biden administrations, while others
showed variations. These changes reflect the evolving circumstances of the pandemic, the
growing importance of vaccines in public health policy, and the complex interplay between
healthcare capacity, political ideology, and public health measures. The variations and
uniformities identified throughout this analysis emphasize the crucial need for public health
approaches to remain flexible and responsive to the evolving dynamics of a global health
emergency. Such observations highlight that, as the landscape of a pandemic shifts—due to
factors like emerging virus strains, varying public compliance with health measures, and the
development of new medical interventions—public health strategies must also evolve. This
adaptability ensures that measures remain effective and relevant, allowing for the protection
of public health in the face of unpredictable challenges and changes in the virus's behavior or
societal responses to it.
3.7.7 Practical Implications: Analyzing Mask Mandates in the Context of Different Influences
The influence on mask mandates during the COVID-19 pandemic underscores the importance
of adaptable and dynamic public health policies. This analysis shows that decisions around
mask mandates are influenced by more than health data alone. Political ideologies, the
capacities of healthcare systems, and vaccination progress have all played crucial roles in
shaping these mandates.

Political leanings have affected the adoption and enforcement of mask mandates, leading to
varied approaches across different regions. Healthcare system constraints have also
influenced these decisions, especially in areas where resources are stretched thin. Moreover,
the rollout of vaccinations has impacted the necessity and stringency of mask mandates, with
increasing vaccination rates sometimes leading to relaxed mandates.
Understanding these diverse influences is critical for developing effective public health
strategies in future emergencies. It highlights the need for policies that are not just
scientifically sound but also consider the broader socio-political and healthcare context. This
approach will ensure public health measures are both effective in controlling disease spread
and pragmatic, taking into account the realities of implementing these strategies in diverse
environments.
3.7.7.1 Implications for Response Toward Public Health Emergency Under Different Political
Parties (Democrats/Republicans):
Political affiliation plays a pivotal role in shaping the strictness of mask mandates,
underlining the influence of divergent governance styles and policy priorities across political
parties. The tendency of Democratic-led states to enforce stricter mask mandates aligns with
their proactive stance on health measures, indicating a prioritization of collective health
security over individual freedoms. Conversely, Republican states exhibit a range of responses,
from lenient to moderate, likely reflecting a balance between safeguarding individual liberties
and economic interests. These variances underscore the complexity of navigating political
ideologies in public health policymaking. Understanding these dynamics is crucial for

policymakers aiming to craft effective health directives that both manage the pandemic's
challenges and resonate across the political spectrum, ensuring comprehensive public health
protection.
3.7.7.2 Addressing Challenges Derived from Discrepancies between Hypotheses and Results
The gap between initial hypotheses and actual findings compels policymakers to adopt a
wider lens in data interpretation and policy formulation. The discovery that stricter mask
mandates often align with higher rates of private insurance coverage necessitates a
reconsideration of preconceived notions regarding health behaviors and the public's support
for health policies. Moreover, the intricate relationship between COVID-19 case rates and the
implementation of mandates suggests that additional variables, such as vaccination coverage,
play a significant role in shaping policy decisions. Embracing this complexity and integrating
it into the policymaking process can significantly improve the tailored response and
effectiveness of health policies, ensuring they are both responsive to and reflective of the
current public health landscape.
3.7.7.3 Contribution to the Studies of Multiple Streams Framework (MSF)
This study enhances the Multiple Streams Framework (MSF) by showcasing the interplay
between problem, policy, and political streams, and their collective impact on policy
decisions like mask mandates. It reveals how the convergence or divergence of these streams
accounts for the varied responses of states to the pandemic. By doing so, it underscores the
MSF's capacity to decipher the intricate and sometimes paradoxical aspects of public policy
formation, especially amidst a rapidly evolving health crisis. This comprehensive research

underscores the critical role of the MSF (Multiple Streams Framework) in analyzing and
understanding the complex policy actions taken during the COVID-19 pandemic. It
demonstrates the framework's robust applicability in dissecting intricate policy decisions and
outcomes. Furthermore, the study suggests that the MSF can serve as a valuable tool for
policymakers in future public health emergencies. By offering a nuanced and
multidimensional perspective, the MSF enables policymakers to more effectively evaluate,
shape, and implement responses that are tailored to the unique challenges of any public health
crisis.
3.8 Conclusion
The central research question of this study is: "Considering the numerous influences on
policymaking, how does the Multiple Streams Framework shed light on the crucial
determinants affecting the stringency of mask mandate policies?" The pursuit of
understanding the determinants influencing COVID-related decisions, particularly the
adoption of mask mandates across U.S. states, has been approached with meticulous analysis
using the multiple streams framework (MSF) as a guiding perspective. Between August 2020
and January 2022, this research dissected the intricate web of factors under the three principal
streams of MSF: problem, policy, and politics. The study highlights the multifaceted nature of
policy-making during the COVID-19 pandemic. Political affiliation, travel restrictions, and
healthcare system capacity consistently influenced the strictness of state mask mandates
during the COVID-19 pandemic. Higher vaccination rates notably correlated with more

lenient mandates, reflecting the crucial role of vaccine distribution in public health policy
adjustments. These findings underscore the complexity of pandemic response strategies and
the necessity for adaptable, evidence-based approaches in public health governance. The
introduction of Pfizer and Moderna vaccines played a crucial role in policy relaxation,
indicating the significant influence of healthcare advancements on policy decisions.
Nevertheless, like all academic endeavors, this study has limitations. Crucially, specific
influential parameters, notably public opinion, could not be incorporated due to the
unavailability of quantifiable data or challenges in consistently summarizing them every
month, rendering them unsuitable as cross-sectional variables. These gaps highlight areas for
potential enhancement in future investigations. While this study has made significant
contributions to its field, the absence of specific vital parameters, such as public opinion,
marks an area for potential enhancement in future investigations. This limitation
acknowledges the inherent challenges in social science research and opens avenues for
ongoing inquiry and development in the quest to achieve a more thorough and nuanced
understanding of complex societal dynamics.
This study contributes significantly to pandemic policy analysis by applying the Multiple
Streams Framework (MSF) to understand the intricate convergence of problem, policy, and
political streams. It offers a novel perspective on the dynamics of public health policy,
particularly in the context of mask mandate policies during a global pandemic. The research
emphasizes the importance of evidence-based decision-making and advocates for a dynamic
policy approach responsive to changing situations. It highlights the need for a comprehensive

policy design that incorporates a variety of factors, such as socioeconomic data, healthcare
infrastructure, cultural norms, and social determinants of health. By extending the MSF's
application to a public health emergency, the study enriches the field of policy studies. It
underscores the importance of considering the interplay between different streams in
developing effective health strategies. Furthermore, the findings offer valuable insights for
future pandemic responses, emphasizing the need for more effective and equitable strategies
in public health emergencies.
As I reflect on the lessons of this pandemic, the insights from this study hold profound
implications for future research endeavors. As the U.S. and the global community inevitably
face public health emergencies in the future, the tapestry of decision-making variables
illuminated in this study could serve as a foundational reference. There remains a compelling
need to evolve our understanding continually, integrating overlooked variables and applying
our learnings to craft more effective and responsive policies in the face of unforeseen public
health challenges. I strive towards a more informed, cohesive, and resilient future through
studies like this.
To incorporate the comparative analysis as a supplement to the conclusion of the third thesis
paper, we can introduce the summary with the following transitional paragraph:
We have unearthed vital comparative insights after thoroughly investigating the distinct
approaches to public health crisis management between China and the United States. These
insights reveal the fundamental differences in governance, policy responses, and healthcare
innovation between the two nations and demonstrate how these differences shape their

respective approaches to handling emergencies. This comprehensive analysis provides a
valuable perspective for understanding the unique models China and the U.S. adopted in
facing public health crises and their outcomes. In what follows, we summarize the key
findings from our three papers, discussing which study results we would expect to differ
between China and the U.S. and exploring the underlying reasons for these differences.
Differences in Governance and Policy Responses: In China, information and policy responses
are controlled from the top down, focusing significantly on mass media management and the
influence of leaders' personal experiences and viewpoints on emergency handling. This
contrasts with the more open and decentralized media environment in the U.S., where various
information sources allow public opinion and expert advice to have a greater impact on policy
formation.
Contextual Influences on Policy Effectiveness: In China, policy effectiveness is influenced by
regional characteristics and strong central directives, while in the U.S., state-level COVID-19
responses are more significantly shaped by political leanings, public opinion and healthcare
advancements, such as vaccine development, rather than by centralized commands.
Impact of Healthcare Innovations: In the U.S., healthcare innovations, particularly vaccines,
have played a crucial role in policy decisions, highlighting the central role of medical
advancements in shaping policy choices. Conversely, China's initial strategy relied more on
stringent control measures, with a slower integration of healthcare innovations into policy
adjustments.

Based on these findings, we anticipate differences in the research results regarding
governance and policy responses, the influences on policy effectiveness, and the impact of
healthcare innovations between China and the U.S. Specifically; these differences could
underscore the roles of centralized versus decentralized decision-making in emergency
responses, the influence of political, societal, and regional characteristics on the effectiveness
of policy measures, and the manner and speed at which healthcare innovations influence
policy adjustments, reflecting the distinct approaches of each country in incorporating
medical advancements into their public health strategies.

