


Evaluating the Frequencies of Self-Reported
Mental Health Conditions in Affluent Youth
Section 1: Foundation of the Study and Literature Review
Introduction
The overall state of mental health in American youth is rapidly deteriorating.
According to the 2017 State of Mental Health in America youth data report, 11% of
youth between the ages of 12–18 reported at least one major depressive episode during
the 2017 calendar year (Mental Health America [MHA], 2018). During the same year, the
National Institute of Mental Health (NIMH; 2017) reported that suicide was the second
leading cause of death among American youth ages 15–24. The concerns associated with
these reports is that both the number of depressive episodes and suicides is up from the
previous year, a trend that has remained consistent over the last decade (MHA, 2018;
NIMH, 2017). With a large number of individuals, including children and youth, from
different cultures, backgrounds, and socioeconomic conditions struggling with mental
health issues, it is evident that mental health is no longer an individual problem. Mental
health has broken the social threshold and been confirmed as a public health concern
(Lee, 2015). Therefore, the issue can no longer be restricted to a private clinical setting.
Instead, there must be a concerted effort to bring awareness and resources to improving
the mental health of youth (World Health Organization [WHO], 2014).
Local health departments across the United States have accepted the charge to
tackle mental health at the community level. The American Public Health Association
(n.d.) has declared the need for public health involvement in mental health to achieve

parity and preserve the needs of future generations. However, even with the best of
intentions, local efforts have been met with challenges due to the dynamic nature of
mental health, especially when considering the many social variables that influence
adolescent behavior (Bøe et al., 2014; Meyer, Castro-Schilo, & Aguilar-Gaxiola, 2014;
Schaefer et al., 2017). While local public health has experienced some small victories in
managing mental health needs, the trending data indicates these efforts are not enough.
Intervention efforts have produced subpar results, and complicated social factors have left
many local public health agencies frustrated and wondering if their efforts are having a
positive impact on the community (Henderson, Evans-Lacko, & Thornicroft, 2013).
Mental health differs from traditional public health in that socioeconomic status is
not a sole predictor of risk or outcomes (Centers for Disease Control and Prevention
[CDC], 2017c; Fink, 2014). This is especially true for youth (MHA, 2018). All youth,
regardless of individual financial circumstances, are at risk of experiencing substandard
mental health outcomes. This ever-present risk defies existing public health theory and
places an immense burden on already limited public health funding (Lee, 2015). One of
the conventional strategies used by local public health agencies to address public health
concerns is the Community Health Assessment (CHA; National Association of County
and City Health Officials, 2017). These data-driven assessments identify the current
health of a community and guide future public health efforts. However, while a local
CHA may capture a mental health need, it is undetermined if CHA-driven interventions
are adequately equipped to improve mental health outcomes. This gap in knowledge

threatens the efficiency of local public health and unintentionally provides a disservice to
individuals, especially youth, struggling with mental health.
Socioeconomic status, poverty, and access to care are proven social determinants
of overall health. They have also been proven to affect mental health, although they
cannot be used as the sole predictors. While it is well known that poverty and
socioeconomic status negatively influence mental health in youth (Elgar et al., 2016;
LeScherban, Brenner, & Schoeni, 2016), much less is known about the role of affluence
on mental health in youth and adults (Schaefer et al., 2017). With studies by Park and
Hwang (2017) and Viner et al. (2012) indicating lower socioeconomic children living in
affluent communities are at greater risk for negative health outcomes, it is unknown if
this model is consistent for mental health in affluent communities.
As the public concern for mental health continues to grow, the role of public
health will continue to evolve. Although most local public health agencies are willing to
and capable of dealing with mental health, it is important to determine if traditional
methods of assessment, like a CHA, are effective. Additionally, further defining the
impacts of socioeconomic status and affluence on mental health are necessary for local
public health agencies attempting to determine the breadth of the problem. Unfortunately,
the matter is more pressing than ever considering the high rates of depression and suicide
ideation in the youth population. Each child deserves an equal opportunity to live a long,
healthy, and happy life. This belief is true for overall health as well as mental health and
should not be predicated on socioeconomic standing. However, the definition and size of
the problem must precede the solution. This research effort must include a commitment to

understanding the current risks and social drivers of mental health across the entire
socioeconomic gradient. Additionally, research must determine if the current methods of
assessment and identification are suited to deal with a problem of this magnitude.
Problem Statement
Mental health is defined as “a state of well-being in which the individual realizes
his or her own abilities, can cope with the normal stresses of life, can work productively
and fruitfully and is able to make a contribution to his or her community” (WHO, 2014).
The CDC (2017) identified mental health as an emerging public health issue, especially in
youth 14–18 years of age. In the United States, improving the mental health of the youth
population has become a top priority for many local public health departments. However,
this task has proven difficult for local public health given the unpredictable and
indiscriminate nature of mental health in children and young adults (Bøe et al., 2014;
Elgar et al., 2014). While socioeconomic standing typically results in improved physical
health outcomes, it does not preclude affluent individuals from experiencing the
challenges related to mental health (CDC, 2017d). This paradigmatic shift from
traditional public health theory, where increased access to care and resources generally
improves health outcomes, makes it challenging for local public health officials to create
effective programs that address mental health concerns using existing public health
models (Soriano, 2013). The stereotypical belief that wealth eliminates risk has presented
challenges to managing the mental health of youth in areas of affluence.
U.S. Highway 40 splits Summit County, Utah, creating a prominent physical,
political, and economic divide between the east and west sides of the county. Nearly 65%

of the population resides on the west side of the county where the rates of affluence are
greater than on the east side. While national reports indicate that Summit County
typically experiences above average health outcomes (County Health Rankings
Roadmaps, 2017; Summit County Health Department, 2012), it is likely that the findings
of these studies do not accurately reflect the sensitive nature of mental health among the
youth throughout the entire county (Piotrowska, Stride, Croft, & Rowe, 2015; Schaefer et
al., 2017; Williams, Priest, & Anderson, 2016). In 2012, the Summit County Health
Department (SCHD) completed a CHA that helped identify a lack of mental health
services and programs in the area, including resources for suicide ideation and
depression, as a primary concern. Among the priority groups were youth between the
ages of 14–18 (hereafter referred to as “youth”). Furthermore, individuals with low
socioeconomic status living in affluent communities experience an even greater gap in
services, placing them at greater risk for mental health problems (Mendenhall, Kohrt,
Norris, Ndetei, & Prabhakaran, 2017).
As a result of these findings, the SCHD implemented countywide intervention
programs aimed at reducing suicide ideation and limiting depressive episodes, while
improving access to mental health services. However, it is unknown if evidence-based
initiatives like “QPR” (question, persuade, refer), which provide students and teachers
with the skills to recognize individuals who are at risk of suicide and then act
accordingly, have reduced the frequency of self-reported of suicide ideation, and “Hope
Squad,” which empowers student bodies to create student alliances aimed at inclusion of
all students and improving morale, have reduced depressive episodes in youth throughout

the county over the last six years. Furthermore, it is possible that the CHA- driven
intervention efforts have resulted in different outcomes in the youth from the east side
compared to the west side, as a result of affluence and socioeconomic status, which could
contribute to the mental health disparities of the youth in Summit County. With local
public health agencies taking a keen interest in the mental health of their youth (United
States Department of Health and Human Services, 2018), it is imperative to provide local
health officials with evidence-based guidance on addressing mental health needs in all
youth. While it is understood that children from all demographics are at risk for poor
mental health outcomes (CDC, 2017a), it is important to determine if the CHA- driven
interventions are effective tools for identifying and addressing the mental health status
and challenges of youth within affluent communities. This research provides evidence of
the potential conflicts between affluence and the mental health status of youth from
affluent families or communities. Unfortunately, there is no research on the connection
between mental health and CHA-driven initiatives for the youth of affluent communities.
Purpose of the Study
The purpose of this study was to determine the effectiveness of CHA-driven
mental health initiatives in reducing the frequencies of self-reported depression and
suicide ideation among the youth in generally affluent communities. As noted by the
CDC (2017d) and Bøe et al. (2014), children of all ages are at risk for mental health
complications despite the socioeconomic standing of the family. While much work has
been done to describe the effects of poverty on mental health outcomes for youth (Elgar
et al., 2016), the outcomes of mental health for youth in affluent communities are lesser

known. Furthermore, there is a gap in the literature describing the correlation between
mental health, grade level, and geographic location in generally affluent areas. My goal
for this study was to fill this literature gap and facilitate an understanding of potential
mental health challenges in the youth of affluent communities. By comparing the
frequencies of occurrence for suicide ideation and depression in the youth of affluent
communities before and after a CHA-driven intervention, by grade and location, public
health practitioners can understand the magnitude of the public health problem across the
entire socioeconomic gradient.
In addition to the scholarly value provided by this study, the results of this
research are critical for local public health agencies operating in affluent areas. As the
focus of initiatives to improve mental health in communities evolves into a local public
health issue, the need for evidence-based research, specific to suicide and depression in
youth, is important for local public health agencies (Lê-Scherban et al., 2016).
Furthermore, there is a need to determine if a CHA is an effective tool for identifying the
mental health needs of a community and if the resulting CHA-driven initiatives are an
effective tool for improving mental health outcomes. As the conversation about mental
health, especially in youth, shifts from a clinical perspective to a public health approach,
using data to facilitate the response is important for social change and removing the
societal stigma associated with mental health challenges. More importantly, it ensures the
efforts to improve outcomes are producing the desired results and providing individuals
with opportunities for help.

Research Questions and Hypotheses
Research Question 1 (RQ1): What is the correlation between the frequencies of
self-reported depression in 8th, 10th, and 12th grade students when comparing the
frequency of responses from postCHA-driven mental health interventions to the
frequency of responses from preCHA-driven mental health interventions in the youth
attending public high school in Summit County, Utah?
Alternative Hypothesis (Ha1): There is a strong correlation between the
frequencies of self-reported depression in 8th, 10th, and 12th grade students when
comparing the frequency of responses from postCHA-driven mental health interventions
to the frequency of responses from preCHA-driven mental health interventions in the
youth attending public high school in Summit County, Utah.
Null Hypothesis (H01): There is no correlation between the frequencies of
selfreported depression in 8th, 10th, and 12th grade students when comparing the
frequency of responses from postCHA-driven mental health interventions to the
frequency of responses from preCHA-driven mental health.
Research Question 2 (RQ2): What is the correlation between the frequencies of
self-reported suicide ideation in 8th, 10th, and 12th grade students when comparing the
frequency of responses from postCHA-driven mental health interventions to the
frequency of responses from preCHA-driven mental health interventions in the youth
attending public high school in Summit County, Utah?
Alternative Hypothesis (Ha2): There is a strong correlation between the
frequencies of self-reported suicide ideation in 8th, 10th, and 12th grade students when

comparing the frequency of responses from postCHA-driven mental health interventions
to the frequency of responses from preCHA-driven mental health interventions in the
youth attending public high school in Summit County, Utah.
Null Hypothesis (H02): There is no correlation between the frequencies of
selfreported suicide ideation in 8th, 10th, and 12th grade students when comparing the
frequency of responses from postCHA-driven mental health interventions to the
frequency of responses from preCHA-driven mental health interventions in the youth
attending public high school in Summit County, Utah?
Research Question 3 (RQ3): Is there a statistically significant difference between
the frequencies of depressive episodes and suicide ideation in the youth (ages 14-18) of
eastern Summit County and the youth (ages 14-18) of western Summit County when
CHA-driven mental health interventions are similarly applied?
Alternative Hypothesis (Ha3): There is a statistically significant difference in the
frequencies of suicide ideation and depressive episodes between the youth (ages 14-18) of
eastern Summit County and the youth (ages 14-18) of western Summit County when
CHA-driven mental health interventions are similarly applied.
Null Hypothesis (H03): There is not a statistically significant difference in the
frequencies of suicide ideation and depressive episodes between the youth (ages 14-18) of
eastern Summit County and the youth (ages 14-18) of western Summit County when
CHA-driven mental health interventions are similarly applied.
Theoretical Foundation of the Study
The theoretical framework that I used for this study was the diffusion of
innovation theory (DOI), which studies the adoption and diffusion of public health

interventions throughout a community (Rogers & Shoemaker, 1971). The DOI is used to
examine how an intervention gains momentum and diffuses throughout a population.
According to the theory, the rate at which the information disperses and becomes
effective is dependent upon the individual’s social characteristics and circumstances, like
culture and socioeconomic status (Glanz, Rimer, & Viswanath, 2015). The point at which
the idea is adopted is influenced by five main factors including the relative advantage
provided, individual compatibility with the idea, complexity of the concept, verification
of the idea, and the observed results from its implementation (Glanz et al., 2015). As a
result, the DOI can be used to predict how innovations are channeled through the social
system, how quickly the message is received, and the success of the intervention
messaging. This has proven helpful in public health when considering elements of social
change as they relate to interventions aimed at injury prevention and cessation practices
(Greenberg, 2006). Successful communication and adoption of health promotion
messaging is an essential link in the efforts to enhance and improve the wellness of
populations and communities. The significant role of the DOI cannot be underestimated
in the effort to solicit consequential messages from leading public health agencies
regarding mental health (Lee, 2015). Additionally, the connection between intervention
efforts and pre-post analysis align with the framework of the DOI. Therefore, the DOI
framework can assist in determining if CHA-driven initiatives are effective for improving
mental health outcomes in the youth of affluent communities.

Nature of the Study
For this study, I used a quantitative method with a quasiexperimental design.
Quantitative research is consistent with a pre-post intervention study design to evaluate
the effectiveness of evidence-based public health programs (Soriano, 2013; Thiese,
2014). Creswell and Creswell (2017) noted that a quasiexperimental design is an effective
means for determining causality where a pre-post test design is used.
This study focused on youth attending public high school in Summit County.
There are three school districts in Summit County, with approximately 2,100 students
aged 14–18. Based on current enrollment numbers for the 2017–2018 school year, there
are 983 students on the east side and 1,119 on the west side of the county. This study will
help the researcher consider frequencies of self-reported suicide ideation and the number
of self-reported depressive episodes among this target demographic. By evaluating
secondary data acquired during the implementation of mental health programs, this
research can help determine whether improvements in mental health outcomes over a six-
year period are consistent and effective for youth attending public high school.
Additionally, the results will be used to determine if the differences in mental health
outcomes between the east and west sides are statistically different as a result of affluence
(Pem, Bhagwant, & Jeewon, 2016).
Literature Search Strategy
My focus in the literature review was to identify peer-reviewed articles and
academic works that addressed the connection between CHA’s, mental health, and public
health among youth populations. My strategy for the literature search was to identify
research relevant to the topic of study using electronic library databases, search engines,

government publications, non-profit organizations, and textbooks from 2003–2018. I
acqired seminal articles using an open-ended search that was not date-restricted.
I used a variety of research databases to search for peer-reviewed articles,
including Walden Library, Academic Search Premier, PubMed, ResearchGate,
MEDLINE, PsycINFO, and Sage Publications Incorporated. The literature search used
Google Scholar and Google as the primary search engines for the literature review.
Government publications from the CDC, the WHO, and the National Institutes of Health
(NIH) provided additional inforamtion for this literature search. The National Association
of City and County Health Officials (NACCHO), American Public Health Association
(APHA), and National Association of Local Boards of Health (NALBOH) provided
information specific to local public health agencies. Textbooks acquired during
coursework provided the theoretical framework and identified suitable statistical tests for
this research.
Search Terms
The following terms were used for the literature search: mental health, public
health, childhood mental health, community health assessment, community- based
participatory research, poverty, affluence, socioeconomic status and mental health,
community mental health, mental health programming, mental health outcomes in youth,
youth suicide, youth depression, income inequality and mental health, diffusion of
innovation theory and mental health, and social determinants of mental health. The review
of texts and reports focused on publications written in English between 2012– 2018.
However, all texts and articles were considered. Articles and textbooks regarding theory,

evaluation practices, and statistical analysis were not date restricted and permitted for use
during the literature review.
Literature Review Related to Key Variables/ Concepts
Mental health is a broad term that defines a variety of emotions related to well
being. To date, much of the work around mental health in youth has focused on
identifying and understanding the risks associated with social inequality (WHO, 2014).
Reiss (2013) found strong similarities in the social determinants as they relate to physical
and mental health. Poverty, violence, domestic instability, and family status all negatively
impact adolescent mental health in families with lower socioeconomic status (Viner et al.,
2012). Although fundamentally different, social stressors have also been found to impact
the mental health of youth from affluent families and communities, resulting in negative
mental health outcomes (Levine, 2008). Family expectations, material desires, and
isolation have been identified as predictors of depression and suicide in affluent youth
(Levine, 2008). These findings indicate the burden of mental health is endemic across all
social structures, from rich to poor, and the perceived benefits of affluence do not
preclude youth from experiencing mental health setbacks (Schaefer et al., 2017). Fink
(2014) believed this subgroup is overlooked and forgotten, limiting our understanding of
the immense need for mental health assistance in affluent youth. Luthar and Barkin
(2012) argued there is far less research evaluating the connection between affluence and
mental health when compared to social inequality and mental health. As a result, it is
possible that the mental health crisis among youth is far greater than originally
anticipated (Schaefer et al., 2017). Furthermore, youth on the lower end of the

socioeconomic scale in affluent communities are at even greater risk than the youth of the
same income bracket living in impoverished or underserved areas (Osypuk & Tchetgen,
2012; Williams, Priest, & Anderson, 2016).
This separation between the privileged and underprivileged creates a void that
allows youth to be overlooked and forgotten until it is too late (Bor et al., 2014).
Additional social stressors could also cause variation in the mental health of children by
grade level as they experience different cultural norms and seek social acceptance
(Cummings, Wen, & Druss, 2013). This potential gap in care grows due to the lack of
understanding on the effectiveness of CHA-driven mental health interventions for all
youth in affluent communities. The connection between affluence and mental health,
along with the use of CHA-driven interventions, must be explored further to gain an
understanding of how intervention efforts aimed at affluent communities with a complex
social dynamic fare in improving mental health outcomes.
Mental Health in Youth
Bor, Dean, Najman and Hayatbakhsh (2014) believed the mental health of
children is under attack. Data provided by the CDC (2017d), the NIMH (2018), and the
WHO (2014) provided evidence of a steady decline in mental health among youth,
especially considering the increase in depressive episodes and suicide. The NIMH
reported in 2017 that suicide was the second leading cause of death in youth, runner-up to
only accidental or unintentional injury. During that same year, the number of youth
reporting at least one depressive episode rose from 8% to 11% in 1 year based on
findings from a national survey (NIMH, 2018). Given this trend, the APHA (n.d.) has

joined the declaration that the preservation and promotion of mental health in youth is a
public health concern now and for the future.
Cummings et al. (2013) and Henderson et al. (2013) believed access to effective
mental health services and social stigma are two of the biggest challenges for youth
dealing with suicide and depression. The cultural stigma of mental health has prevented
teens from seeking services when available, and the social pressures of adolescent society
have forced them to keep their emotions internalized, which adds to other emotional
problems that may already exist (Piotrowska, Stride, Croft, & Rowe, 2015). Bor et al.
(2014) suggested that this is not specific to any one socially constructed group, but rather
it is the result of limited resources to deal with an increasing problem. Therefore, rich or
poor, all youth are at risk of experiencing substandard mental health outcomes. As a
result, the effects of mental health are carrying over into adulthood as these youth enter
college and the workforce (Lê-Scherban et al., 2016).
Youth from affluent communities have above average health outcomes but face
similar mental health outcomes as youth living in poverty and social inequality situations
(Meyer, Castro-Schilo, & Aguilar-Gaxiola, 2014). However, the mental health struggles
of affluent youth are often forgotten and overlooked given their social standing and
dogmatic belief that their needs are being met (Luthar, 2003). While affluent youth may
not be at risk in a traditional sense when compared to other children in different economic
positions, when considering their vulnerability and need, the risk of suicide and
depression remains high (Luthar & Barkin, 2012). Therefore, research efforts to
understand the challenges faced by affluent children should compare to those of work

being conducted on the correlation between economic inequality and health outcomes. As
predicted by Schaefer et al. (2017), until we fully understand the extent of mental health
in all youth, we cannot begin to implement programs that create immediate social change.
Predictors of Mental Health in Youth
Predictors of mental health in youth can range based on social structure, economic
position, geographic region, and individual resiliency (Mendenhall et al., 2017). Although
these predictors are fairly consistent in all aspects of health, the social factors present in
affluent situations should not be discounted given their tremendous effect on mental
health (Levine, 2008; Luthar & Lantendresse, 2005). Multiple studies have shown that
privileged children are suffering from high rates of depression, anxiety, and substance
abuse (Levine, 2008; Reiss, 2013; Viner et al., 2012). Additionally, children living in
affluent situations can feel isolated given the lack of parental commitment and
involvement in life experiences (Viner et al., 2012). Fink (2014) cited the stress caused
by family affluence, expectations, and career selection as a direct predictor of depression
and suicide in young adults attending college. In early studies, Luthar (2003) indicated
that a social shift in the traditional family structure and the lack of parental investment in
fostering a family environment would have dire impacts on the mental health of children
from wealthy families. Luthar supported this prediction with the 2005 paper indicating a
shift was occurring and children with affluent upbringings were being forgotten. Finally,
in 2012, Luthar and Barkin noted that an entire subpopulation had been overlooked and is
now experiencing rates of suicide and depression that deserve immediate attention. Given

these findings and predictions, there is evidence that affluence is a predictor of poor
mental health in youth.
Depression in Youth
Due to the changing levels of hormones associated with puberty, the volatile
nature of the youth social structure, youthful inexperience, and anxieties caused by the
educational component of school, many of the symptoms used to describe depression
might be expected in youth between the ages of 14–18 (Hawton et al., 2013). However,
these natural feelings associated with development into adulthood should not be confused
with depression or depressive episodes. A depressive episode is defined by feelings of
severe anxiety, emptiness, hopelessness, worthlessness, guilt, and inadequacy that result
in insomnia, loss of appetite, and the inability to perform everyday functions (NIMH,
2018). These symptoms last for an extended period of time, generally 2 weeks or more,
and are not resolved on their own. These feelings are immune to interactions with the
outside world and often become worse as a result of them (CDC, 2017c). While mild
symptoms can be expected during a break-up or exam season, the consistent and strong
nature of these symptoms do not persist as they do in youth experiencing a significant
depressive episode (Cummings et al., 2013).
In 2017, one in 10 children experienced an extended depressive episode (NIMH,
2018). Levine (2008) noted that affluent children have higher rates of depression than any
other group of young people in the United States. However, despite the perception that
resources are available to manage mental health, less than 5% of the affluent youth
receive professional help (Hawton et al., 2013). Even worse, a high percentage of these

youth have considered or attempted suicide, making depression the number one risk
factor for suicide in affluent youth (CDC, 2017c; Fink, 2014; NIMH, 2018; Schaefer et
al., 2017; Viner et al., 2012; Williams et al., 2016).
Suicide in Youth
Suicide is the second leading cause of death in youth ages 12–18 and the second
leading cause of death for individuals between the ages of 10–24 (CDC, 2016). More
teenagers die from suicide than cancer, heart disease, pneumonia, influenza, and drug
overdose combined (CDC, 2017d). According to the CDC (2016) and the NIMH (2017),
suicide in youth has nearly tripled since 1940. Levine (2008) cited that much of this
increase has occurred in the youth of affluent homes and communities. The risk factors
for suicide include depression, a family history of mental health problems, access to
lethal means, alcohol and drug use, exposure to suicidal behavior by others, and
underdeveloped social skills (Hawton et al., 2013).
Although most teens, especially girls, are unlikely to convey feelings or intent to
commit suicide, certain trends have emerged. The CDC (2016) noted that of the reported
suicides for youth between the ages of 10–24, 81% were boys and 19% were girls.
According to preliminary data provided by the Utah Department of Substance
Abuse and Mental Health through the Student Health and Risk Prevention Survey
(SHARP), overall Utah ranks number five out of 50 for rates of suicide (SHARP, 2018).
When considering youth-specific data, Utah has a suicide rate of 13.15 per 100,000
individuals (SHARP, 2018). Furthermore, the NIMH (2017) believed that in almost
100% of the youth suicide cases, the deceased youth displayed at least one symptom that

might indicate the individual was struggling with suicidal tendencies. Unfortunately, it is
estimated that only one in 47 teens who are contemplating suicide consider using
suicidespecific resources (CDC, 2016).
For those who have attempted suicide and survived, the majority of them find
themselves in a similar position at a later date if they do not receive treatment and help
(Elgar et al., 2016). This increases the need for program evaluation aimed at reaching
atrisk populations, including affluent youth. Bor et al. (2014) noted that mental health
problems, including suicide, are dramatically increasing among the youth population, yet
little has changed in how health advocates have approached the problem. This may
indicate that CHA-driven interventions are inadequate to deal with a problem of this
magnitude on any socioeconomic level. While it has been determined that affluent youth
are at an increased risk of suicide when compared to any other youth subgroup (Luthar &
Barkin, 2012), it is less understood if public health intervention strategies are an effective
approach to this painful truth.
The Culture of Affluence
Wealth presents unique opportunities for affluent youth that are not available to
children from other socioeconomic classes (Osypuk et al., 2012). While this statement
comes as no surprise to public health professionals, it is an important fact that deserves
further consideration. In most cases, affluence presents opportunities that result in better
health outcomes, better schooling, a safer community environment, and material
possessions—like cars and cellphones—that increase quality of life (Lund & Dearing,
2013). However, this culture of affluence can lead to behaviors that destroy individual

mental health while negatively influencing the mental health of those around the
individual (Yoshikawa, Aber, & Beardslee, 2012).
Additionally, children from wealthy families have high rates of substance abuse
and underage drinking and are sexually active at early ages (Viner et al., 2012). Luthar
and Barkin (2013) believed these risky behaviors are the result of increased access to
such items as a result of additional financial means or minimal supervision from absent
parents. This additional money can promote feelings of privilege and superiority over
students from families of lesser economic means. This belief is further supported by acts
of bullying and isolation by affluent teens against their peers from less affluent families
(Yoshikawa et al., 2012). Each of these unhealthy behaviors can lead to depression and
are sometimes considered an outward expression of an internal cry for help (Levine,
2008).
In some instances, the family structure of affluent families can experience
struggles that mirror single-parent homes or homes with domestic instability. Although
these teens are not at risk of financial instability, it is not uncommon for parents to lack
the day to day interactions with their children that are important for social, emotional, and
physical development (Elgar et al., 2013). Parents in affluent communities or homes may
be career driven which can limit their time at home. Even when both parents are in the
home, personal ambitions and individual interests can rank higher than being involved
with children or understanding the needs of the child (Viner et al., 2012). This results in
missed opportunities to establish bonds between parents and children, making it more
difficult to create a relationship as the child grows into adulthood.

According to Lund and Dearing (2013), growing up in affluent areas presents
risks associated with a constant connection to peers through social media and other
technology platforms. Unlimited access to the internet means youth with cell phones and
other devices are constantly evaluating the social dealings of their peer network. Rarely
are these youth seen without their cell phones, and it is common to engage in social
media banter several times a day (Schaefer et al., 2017). This constant exposure limits the
youth’s ability to detach from the electronic world and exposure to potentially harmful
interactions. The inability to escape social media presents a constant barrage of
information that is perceived as factual and consequently used to evaluate oneself (Bor et
al., 2014). These experiences can be both good and bad. However, when the use of social
media results in mistreatment, bullying, or intentional harm to an individual, either
emotional or physical, the inability to remove one's self from this harassment
dramatically increases the risk of depression and suicide (Lê-Scherban et al., 2016).
Although this form of mental abuse occurs in all youth, the material possessions and
resources that are available to affluent youth provide increased access to various social
media platforms at an early age. This constant connection through cell phones, tablets,
and other means of mobile electronic access make it nearly impossible for youth to
escape the negative influences found on social media. As a result, their perception of
reality is formed through the content on social media, which can have negative
consequences on mental health (Olfson, Druss, & Marcus, 2015).

Affluence and Mental Health in Youth
Luthar and Lantendresse (2005) noted that affluence presents various
psychosocial risks to children. Levine (2008) supported this claim by providing evidence
of increased risk of depression, anxiety, substance abuse, and social disorders among
youth 12–18. Levine (2008) added that the constant pressure of achievement and
emotional and physical isolation between children and parents in affluent situations can
dramatically increase rates of depression and suicide. This contradicts the stereotypical
belief that children of wealth are at low risk, and children of poverty are at high risk.
Piotrowska et al. (2015) argued that all children, regardless of socioeconomic standing,
are at risk of mental health problems. Luthar (2003) and Luthar and Barkin (2012)
provided compelling evidence that affluence has been a driving factor for suicide and
depression in youth for a considerable amount of time. Recent studies by Lund and
Dearing (2013) and Schaefer et al. (2017) indicated that early predictions about failing
mental health in affluent youth are being fulfilled. Just as children of poverty were
ignored by researchers in the 1960’s and 1970’s, research on the mental health of affluent
children has been limited, in comparison to other studies involving mental health, based
on the stereotypical belief that this subgroup was at low risk given their socioeconomic
standing.
While wealth and resources typically result in better outcomes, it does not
guarantee that individuals will seek the help that is available. Ibrahim, Kelly, and
Glazebrook (2013) found that college-level youth of affluent families do not seek help or
utilize resources for mental health issues for fear of disappointment or ridicule from

family members. Park and Hwang (2017) had similar findings in their assessment of
Korean youth who avoided reporting feelings of depression or anxiety to their parents so
they would not bring embarrassment upon the family name. Bøe et al. (2014) posited that
parents and their level of support is the number one reason youth seek help for mental
health problems. However, if children are isolated from parents, this level of support does
not exist. Elgar et al. (2013) noted that the availability of resources does not ensure youth
will receive the necessary treatment for mental health problems, even when parents are
closely involved with children. This presents a similar risk to that of children in lower
socioeconomic positions when resources are not available. Regardless of the barrier, be it
lack of resources or the avoidance of existing resources, the outcomes of suicide ideation
and depression remain despite socioeconomic position.
Community Affluence and Mental Health of Youth
The culture of affluence also presents challenges as it relates to social perception
and the community. Sometimes referred to as “keeping up the with Jones,’” the pressure
to remain popular, relevant, and consistent with the latest social trends creates additional
pressure that may evoke stress and mental health problems for both parents and children
(Julien, Richard, Gauvin, & Kestens, 2012). While the health implications of
neighborhood and community structure are well-known indicators of health, affluence is
generally not considered a risk factor for mental health. However, based on early
indications from preliminary studies, it appears that affluent communities may present the
same risk as other communities with a history of poor mental health outcomes in youth.

Solari (2012) suggested that neighborhoods across the United States have
undergone dramatic change over the last decade. While affluent neighborhoods continue
to provide physical safety and promote physical activity, the core of the personal
connection between neighbors, friends, and community is deteriorating (Solari, 2012).
However, it is difficult to define a faltering human connection at the broader social level
and it is unknown if the downfall of the American neighborhood is somehow connected
to the increase in mental health problems among youth. For those that believe it takes a
village to raise a child, this could be true. Solari (2012) suggested additional research is
needed and warranted.
Those living in affluent areas typically value the presentation and social status of
their neighborhood over the sense of community. This individualistic dynamic can
facilitate a false sense of mental safety and well-being. Furthermore, this isolating
behavior can carry over to the children, as they too are isolated from others in the
community (Meyer, Castro-Schilo, & Aguilar-Gaxiola, 2014). Additionally, wealthy
children who are isolated, both physically and emotionally, may develop psychosocial
problems that directly contribute to depression or may lead to suicide. However, these
risk factors are often ignored under the pretense that wealth minimizes risk. Lund and
Dearing (2013) believed that being raised in an affluent community presents its own risks
for youth and these children deserve special considerations. Levine (2008) believed the
price of privilege is more than the material cost but extends to include the mental health
of youth in these areas. Luthar and Barkin (2012) suggested that while the mental health
risks associated with wealthy neighborhoods are better understood, additional research is

needed to determine how best these youth are served and how efforts to improve mental
health can overcome the barriers of wealth and affluence.
Family Affluence and Mental Health in Youth
Luthar (2003), Levine (2008), and Elgar et al. (2016) cited isolation and family
pressure as risk factors for suicide and depression in youth ages 12–18. Isolation occurs
as a result of the parents’ perception of what is best for their child. Although this concern
exists, it is not the intent of the parents to place their child in this position. The pursuit of
career goals, community involvement, or advanced education requires valuable time.
These pursuits are not rooted in greed or individual accomplishment; rather they are taken
up with the idea that they provide additional and better opportunities for the child (Julien
et al., 2012). However, this commitment to providing the child with material possessions
and wealth comes at a cost. While the parents believe they are doing what is best for the
child, the child does not understand the connection between the wealth, time, and the
absence of the parents (Levine, 2008). Instead, the perception of the child is formed by
the limited interaction with his/her parents. Therefore, the cost to provide for the child is
more than just time; it can present challenges that relate to mental health that may
manifest in different ways later in life.
Family pressure is another risk factor for mental health problems in the youth of
affluent families. Fink (2014) noted that family pressure to select a prestigious institution,
be successful both in school and thereafter, and pursue the appropriate career path all
affected the mental health of American college students from wealthy families. Ibrahim et
al. (2013) found that similar family pressures on college students resulted in increased

rates of depression in the UK. These pressures may stem from a variety of social
constructs, both historical and current. However, their presence in the conversation about
mental health in the youth of affluent communities cannot be ignored. Levine (2008)
reported that fear of failure or disappointment is typically reported by youth who
attempted suicide and failed. In some cases, the parents were unaware that pressure or
expectations even existed (Lê-Scherban et al., 2016). Nonetheless, family affluence
results in family pressure, and both must be considered when addressing the mental
health of affluent youth.
Operational Definitions
Affluence: For this study, affluence is defined as the median income being greater
than 40% above the national median income (Solari, 2012). Summit County’s median
income is $91,470, compared to the national median income of $59,039 (United States
Census Bureau, 2017) placing it at 54.93% above the national average. Affluent
neighborhood advantages include safety, high-quality schools, proximity to jobs,
increased physical activity, and access to health care services (Luthar & Barkin, 2012).
Community Health Assessment-Driven Interventions: Mental health interventions,
like “QPR” and “Hope Squad,” that originated from the findings of a CHA that are
intended to address and improve the deteriorating mental health of youth using a public
health approach.
Depression: A common but serious mood disorder. It causes severe symptoms
that affect how you feel, think, and handle daily activities, such as sleeping, eating, or

working. For a person to be diagnosed with depression, symptoms must be present for at
least two weeks (National Institute of Mental Health, 2018).
Mental Health: The state of emotional, behavioral, and social maturity or
normality that influences the emotions, feelings, and behaviors of an individual (National
Institute of Mental Health, 2018).
SHARP Survey: The Student Health and Risk Prevention (SHARP) statewide
survey is administered every two years to students in grades 6, 8, 10, and 12 in all public
school districts across Utah. This voluntary survey is designed to assess adolescent
substance use, antisocial behavior, and the risk and protective factors that predict these
adolescent problem behaviors, including depression and suicide (Utah Department of
Human Services, 2018).
Socioeconomic Status: The social standing or class of an individual or group
(American Psychological Association, 2018). It is often measured as a combination of
education, income, and occupation. Examinations of socioeconomic status often reveal
inequities in access to resources, along with issues related to privilege, power, and control
(Elgar et al., 2016).
Suicide: Death caused by self-directed injurious behavior with intent to die as a
result of the behavior (NIMH, 2017). Suicide is the second leading cause of death for
youth between the ages of 10 and 24 and results in approximately 4,600 lives lost each
year (CDC, 2017d). Deaths from youth suicide are only part of the problem. More young
people survive suicide attempts than actually die (Reiss, 2013).

Youth: The United Nations (n.d.) defines youth as individuals between the ages of
15–24. For this study, the term youth describes the age group of children 14–18 years of
age attending public high school in Summit County, Utah in order to capture those
students transitioning from eighth grade to ninth grade who are 14 years of age.
Assumptions
The following assumptions were made in this study:
1. The SHARP dataset resulted from a truly cross-sectional study that provides
quality data through anonymous participation in the survey for all youth
attending high school between the ages of 14–18 in Summit County, thereby
increasing the quality of the data and reducing potential bias.
2. Data entry was done in the most efficient and effective manner to limit errors.
3. Missing data from the original dataset were completely at random, and the
absence of information did not bias the results of the study in any way, even
when listwise deletion, pairwise deletion, or hot deck imputation data cleaning
techniques were used by the original researchers (Langkamp, Lehman, &
Lemeshow, 2010).
4. The youth participants in the study answered the questions honestly and free
of bias.
5. The youth participants in the study were residents of Summit County, Utah
between the ages of 14–18 years of age attending high school.
6. The expected dependent and independent variables were contained within the
secondary dataset used for this study.

7. The dataset holders willingly released the dataset for this analysis upon
request.
8. The datasets had enough responses and variables for an unbiased analysis.
Considering these assumptions enhanced the validity of the study.
Limitations
The following limitations of this study are hereby acknowledged:
1. This study used secondary data for analysis. Therefore, the available data
were not collected to address this particular study’s research questions.
2. The SHARP survey is voluntary, which could affect the inferences drawn
from this study.
3. This dataset includes seven years of survey data (2011–2017). During that
time, the level of mental health awareness may have changed due to notable
events around youth depression and suicide ideation.
4. Individual perceptions about what defines a depressive episode and suicide
ideation may have skewed the answers provided by survey respondents.
5. The normal hesitation of youth participants to share individual experiences
may influence the findings of the study even when surveys are anonymous.
This limitation must be considered when using secondary datasets involving
youth participants (Creswell & Creswell, 2017).
Scope and Delimitations
This study was based on the SHARP statewide survey dataset that evaluated
depression and suicide ideation in youth ages 14–18 for the years 2011, 2013, 2015, and

2017 and was delimited to a quantitative cross-sectional study. The data used for this
analysis are specific to Summit County, Utah and do not include other jurisdictions in the
State of Utah. By using a secondary dataset, there was no primary data collection or
contact with the participants of the survey. This resulted in the study being delimited to
the information collected during the initial research project. All private and protected
information (i.e., name, gender, home address) was removed from the dataset provided
for this study. The sample population was inclusive of all youth between the ages of 14–
18 attending high school in Summit County. Although the survey was completely
voluntary, 3,581 responses were received over the seven-year period. The survey
responses were not selected at random during data collection. Instead, all completed
surveys were included as part of the dataset. All survey responses from youth in Summit
County were included in the data analysis given the focus on the youth in the geographic
region.
Significance
The purpose of this study was to determine if mental health initiatives based on
the findings of a CHA are capable of effectively addressing suicide and depression in the
youth of affluent communities like Summit County. In 2013, one year after the Summit
County CHA, the first mental health programs, like QPR and Hope Squad, were
presented to the three different high schools. Since that time, a variety of CHA- driven
programs aimed at improving mental health within the high schools have been
implemented. However, the effectiveness of these programs has never been formally
evaluated. Given the selected time frame of the study, this research will evaluate seven

consecutive years (2011–2017) of youth-specific data for suicide ideation and depression
by grade and by location to determine the effectiveness of these efforts. As a result, the
findings will help determine if affluence is a barrier to CHA-driven mental health
initiatives among the youth population.
Evaluating the effectiveness of a project pre- and postimplementation is
considered best practice for any public health effort (Davis et al., 2014; Hill et al., 2017).
Per the direction provided by Thiese (2014), one year of preimplementation data
supported by multiple years of postimplementation data with a large sample size for
evaluation is sufficient. In the case of this study, five years of postimplementation data is
provided with a sample size of more than 5,000 youth attending public high school.
Therefore, the timeframe for evaluation would appear adequate for public health
programming given the parameters established by Thiese (2014).
This study builds upon the growing body of evidence that focuses on the
connection between mental health and public health and the need for evidence-based
action by local health agencies. On a fundamental level, such a study is needed to
determine the effectiveness of the SCHD’s intervention efforts in comparison to the CHA
goals set in 2012. The scholarly value of this research is an expanded understanding of
the mental health improvements across the east and west sides of the county where
personal economic position is a potential barrier to mental health services and mental
health outcomes. This research can provide the SCHD and other local public health
agencies with insight into the power of the CHA tool to identify and address the mental
health needs of affluent communities. Furthermore, it can provide evidence that supports

efforts to improve mental health in the community by the health department
administration, fosters public support, and justifies the use of taxpayer funds for public
health programs (Crosby, Salazar, & DiClemente, 2011). With mental health problems
affecting youth across all levels of the socioeconomic scale, it is imperative to determine
if CHAs are an effective tool for local public health agencies operating in diverse
socioeconomic communities.
Evaluating the pre- and postintervention changes regarding suicide ideation and
depression in the youth of Summit County will provide an added understanding of the
social variables, like culture and affluence, which influence mental health outcomes for
the youth in affluent communities. Regardless of the outcome of the study, this
information can provide the SCHD and possibly similar local health departments, where
affluence is a confounding variable, with an evidence-based approach to guide and direct
public health interventions focusing on mental health. As a result, future public health
efforts can be developed to ensure that all of the youth across the entire socioeconomic
gradient are equally represented in public health programs intended to evoke equitable
social change.
Summary and Conclusions
Mental health is an important aspect of overall health. Establishing a healthy
connection between one’s mental state and the body is fundamental to a happy, healthy,
and fulfilling life. Much like a healthy diet and exercise are necessary for optimal
physical health, managing and nurturing mental health is critical for optimal emotional
health. This is especially true for children and young adults as they grow and develop into

adulthood. Providing youth with the necessary tools to manage their own situations is the
first priority in reducing the rates of depression and suicide ideation. At a time when
concerns for mental health are warranted, the youth must feel comfortable in seeking help
for feelings or emotions that do not solicit happiness but detract from the overall quality
of life. A firm understanding of the problem at hand is needed to enact positive social
change. This is accomplished by identifying the breadth of the problem across the entire
socioeconomic strata and evaluating the effectiveness of the intervention programs
specific to the youth contingency.
Mental health continues to be a somewhat taboo subject. Although the discussion
surrounding mental health has been advanced in recent years, those who struggle with
mental health or mental illness still feel isolated and alone (Henderson et al., 2013).
Traditionally, mental health has been dealt with in a professional clinical setting aimed at
treating the individual. This covert approach has allowed a dark cloud to reign over the
subject without addressing the social aspects of mental health (Schaefer et al., 2017),
which has contributed to the hesitation in tackling mental health on a larger scale. Mental
health is not only the result of individual feelings, but it is the culmination of the built
environment, experiences, culture, and other social constructs that form an identity. More
importantly, mental health is the result of individual perceptions about one’s value,
contribution, and happiness. When these individual views are misinformed, skewed, or
inaccurate, a person’s mental health is at risk. However, just like the common cold can be
managed until physical health is restored, lacking mental health can be restored with
proper treatment and care when identified early in the process (Henderson et al., 2013).

Unfortunately, with the large increase in depressive episodes and suicide among youth in
the last five years, it appears as though current efforts are not reaching the youth early
enough in the process. This has resulted in a problem that has outgrown the
individualized care setting and crossed the social threshold into a public health concern.
While the clinical aspect of treatment is necessary for providing care, a public health
approach is needed. This combination of private health and public health is vital to
improving mental health and arming children with the tools and skills for improving
mental health.
Public health offers a variety of resources that are not otherwise available to
individuals struggling with mental health. This is especially true for individuals without
the means to seek private, individual treatment. Although private clinicians play an
important role in mental health, they are client- based. The role of the licensed clinician is
similar to a medical doctor in that patients seek their services for treatment.
Unfortunately, these services can be expensive and require a commitment of monetary
resources that might not be available to families on the lower end of the socioeconomic
scale living in highly affluent areas. Additionally, interventions are based on individual
circumstances. The treatment is tailored to meet the needs of the individual based on the
assessment of the mental health professional. This customized approach is not meant to
improve the mental health of a specific demographic or select group of individuals.
Instead, the focus is on the individual client. This model is used for treating mental health
for those that can afford services through cash payment or insurance providers. However,
this option of treatment is limiting and not available to everyone. Lack of insurance and

costly fees for services rendered make it difficult, if not impossible, for many. Therefore,
public health messaging and publicly funded intervention strategies are the only help for
some. These public health efforts complement what is being accomplished in the private
practice setting and provide an opportunity for a more robust and comprehensive
approach to dealing with mental health, but only when the intervention programs are
evaluated for applicability across all demographics.
In addition to increasing public awareness, public health has the power to remove
the social barriers associated with mental health. The recent declaration by the world’s
leading public health agencies has placed public health on the front line of improving
mental health with special emphasis placed on the youth worldwide. A review of the
recent reports by Mental Health America (2017) and the NIMH (2017) indicates that
early efforts by local public health agencies are failing the youth. Like any other
underperforming public health intervention, assessment and analysis at the local level are
needed. This evaluation of local efforts is not only socially responsible, but it is also
important for improving the state of mental health in the at-risk youth demographic.
Reports by the CDC (2017), the World Health Organization (2017), the American
Public Health Association (2015), and NIMH (2015) have identified youth, especially
those in high school, as an at-risk population. Unfortunately, this declaration is as broad
and non-selective as it sounds. While some data indicate elevated levels of depression and
suicide in youth living in poverty, a majority of the current literature identifies all youth
as at-risk despite individual social circumstances. While CHAs have proven successful in
other areas of public health, it is unknown if these same outcomes can be expected when

considering mental health initiatives. This lack of knowledge has left public health
scrambling to resolve the issues surrounding mental health.
As eluded to earlier, most of the work around mental health in youth has been
focused on the underserved populations on the lower end of the socioeconomic scale. The
pressures of poverty, violence, gangs, drugs, and culture have all been identified as
detractors of good mental health. Additionally, the lack of resources and access to mental
health care exacerbate the problem, limiting the youths’ abilities to manage their own
mental health. However, questions about the impacts of CHA-driven mental health
interventions on youth in affluent areas where resources are available remain. Minimal
research has been done to understand what triggers depression and suicide ideation in
youth on the opposite end of the socioeconomic scale when the social and cultural
triggers associated with poverty are absent. Julien et al. (2012) found that income
expectations, family commitments, and social norms impacted mental health outcomes in
middle to upper class working adults. Hawton et al. (2013) noted workplace stress, job
status/ importance, and social standing were predictors of depression in adults coming
from affluent families. Fink (2014) and Ibrahim et al. (2013) had similar findings
reporting that wealthy college students identified family expectations, school major,
social structure, and job placement as affecting individual mental health outcomes.
Although many of these social predictors are specific to individuals with increased
socioeconomic status, the outcomes of depression and suicide ideation are the same.
The problems associated with mental health cannot be addressed until public
health practitioners, as the new stewards of mental health, determine the extent of the

problem. This evaluation includes the youth of affluent areas. This is especially true as
mental health interventions take an upstream approach to early identification and helping
of youth learn to manage depression. Furthermore, the need to determine how the youth
of affluent areas respond to public mental health interventions is warranted. This research
study enhances our overall understanding of the current mental health status of all youth
and adds to the existing literature on mental health among the youth group. Additionally,
it adds to the existing literature and expands upon the understanding of depression and
suicide ideation in the youth category, which is critical given the dire results of recent
reports. The findings of this study will provide local public health agencies with
evidence-driven guidance for dealing with mental health in the youth of affluent
communities. Coupling these findings with the existing literature base provides local
public health agencies operating in almost any socioeconomic climate a more
comprehensive understanding of mental health among youth ages 14–18.
As public health continues to navigate deeper into the throngs of mental health,
evidence-based guidance is needed. As local public health continues the frontline
approach to administering programs aimed at improving public health, they too will need
data to support their efforts. However, these data can not focus on an extremely diverse
subgroup that experiences somewhat unpredictable behavior due to puberty and
maturation. Instead, the literature must provide a comprehensive and inclusive reference
to all youth across all social structures. Currently, there is a gap in the literature when
considering youth from affluent communities. However, this research helps to fill that

gap and provides an understanding of how public health can evoke positive social change
in the youth across the entire social strata.
Section 2: Research Design and Data Collection
The purpose of this quantitative study was to examine the association between
mental health and the youth attending public school in affluent communities where
CHAdriven interventions have been applied. The researcher analyzed the relationship
between the frequency of self-reported suicide ideation and depression and the
geographic region in Summit County (east versus west) and frequency of self-reported
suicide ideation and depression and high school grade level in the public school system
when CHA- driven interventions are equally applied. This section includes descriptions
of the design, methodology, operationalization of variables, threats to validity, ethical
considerations, and the data management process that I used for this research.
Research Design and Rationale
I used a quasiexperimental design for this research. A quasiexperimental design is
the same as a classic controlled experimental design with the only difference being that
additional statistical controls must be considered because the subjects cannot be randomly
assigned (Creswell & Creswell, 2017; Thiese, 2014). According to Glanz et al. (2015),
quasiexperimental research is consistent with a quantitative pre-post intervention study
design to evaluate the effectiveness of evidence-based public health programs.
Furthermore, Creswell and Creswell (2017) noted that a quasiexperimental design is the
most effective means of determining causality where a pre-post test design is used.

A quasiexperimental approach has many benefits for research using secondary
data. Quasiexperimental designs are less time consuming and can maximize available
resources and expedite the analysis of secondary data. Additionally, a quasiexperimental
design allows the study to be replicated, even when traditional control measures are
missing (Kontopantelis, Doran, Springate, Buchan, & Reeves, 2015). This level of
control is important for research where repeated measures are necessary to determine the
effect. The ability to replicate the findings of a quasiexperimental design increases the
validity and reliability of the study, which is important in all research. The additional
control afforded by a quasiexperimental design using secondary data extends to the
variables of suicide, depression, zip code, and grade as well, again increasing the
reliability of the study. As a result, the quasiexperimental design can account for lack of a
true, randomized study by implementing controls, such as complete inclusion to reduce
selection bias and respondent weighting, which allow inferences to be made about
causality in a timely and efficient manner, an attribute that was important to the outcome
of this study.
The survey was administered to all youth without prejudice or selection.
Therefore, a random selection process could not be established. In lieu of a true
randomized selection process, a pre-post evaluation model, which is consistent with a
quasiexperimental design, was used where all survey respondents were included in the
analysis of suicide ideation and depression before and after exposure to the CHA driven
interventions in the high school youth of Summit County. The control was then compared
to the frequency of self-reported suicide ideation and depression postintervention effort.

As noted by Schweizer, Braun, and Milstone, (2016) a research design of this nature,
using a pre-post evaluation technique, can benefit from a quasiexperimental design,
providing additional validation for its use in this research.
I used secondary data provided by the SHARP database for this study. The use of
secondary data presents many benefits to the researcher including access, efficiency, and
effectiveness. First, the selection of the SHARP dataset provided access to relevant and
timely information about suicide ideation and depression in the youth of Summit County,
making it both cost-effective and highly beneficial to the research. Second, the secondary
data also provided both historical and current information that could not otherwise be
collected retrospectively at the individual level. In a study such as this, where the ability
to analyze historical data is paramount to the outcomes, secondary data are the only
viable option. Third, the use of secondary data eliminates the ethical issues associated
with primary data collection and ensures the confidentiality of the survey respondents.
Finally, secondary data can be easily formatted, and statistical analysis can be executed
quickly, increasing efficiency and reducing the amount of time spent analyzing data. The
SHARP dataset is a large, robust, and comprehensive secondary dataset that offers all of
the benefits above while providing the necessary variables for this research.
Methodology
An explanation of the methodology used to perform the study is provided in the
following subsections. A description of the target population, data management practices,
sampling techniques, instrumentation and operationalization constructs, data analysis
plan, threats to validity, and ethical procedures are included in this section.

Target Population
The SHARP database is a collection of data gathered by the Prevention Needs
Assessment (PNA) survey. The PNA survey is administered every 2 years to students in
6th, 8th, 10th, and 12th grades in most public and certain charter school districts in Utah
(UDHS, 2018). The SHARP survey is a voluntary survey designed to assess adolescent
substance abuse, identify antisocial behavior, and understand mental health challenges in
Utah’s youth to predict adolescent problem behaviors. The voluntary survey is
administered to students in each school district throughout the state. The data are then
further categorized by individual schools within each district, which allows for analysis
between schools within the same district.
For this research, the SHARP survey data from 2011, 2013, 2015, and 2017 for
Summit County were used. The target population was all youth between the ages of 14–
18 who are in 8th–12th grade in Summit County. On average, this survey generates 1,100
responses in Summit County from the target population each year of the survey. The
statistical analysis included all completed surveys from students who are residents of
Summit County. Although the survey included questions about substance abuse, sexual
activity, and antisocial behavior, the research only considered data for depressive
episodes and suicide ideation. Grade and location were the only personal identifiers used
for this research. All other personal information was removed from the dataset as it was
not necessary.

Sampling Techniques
The PNA survey was developed by the Center for Substance Abuse (CSA) to
provide sound evidence of youth risk levels in a community (Utah Department of Human
Services [UDHS], 2018). Different versions of the PNA have been used throughout the
United States for decades with great success. The PNA survey tool has helped state and
local health agencies develop effective prevention services at the regional level (UDHS,
2018). The PNA survey anonymously measures 17 risk factors and 10 protective factors
and inquires about alcohol, tobacco, and other drug use (ATOD). Additionally, the PNA
collected data on mental health issues, such as suicide ideation and depressive episodes,
which provided the information that is specific to this research. In total, the survey used
127 questions to measure 366 items to gather risk information about youth in the State of
Utah. The results of the PNA survey are formatted for the Utah SHARP dataset, which
was used for this research.
Utah State Law requires current legal parental consent at the start of each school
year for students to participate in voluntary surveys that are not considered part of the
school curriculum. Therefore, the PNA survey is officially considered an opt-in activity
and students are not obligated to participate. The opt-in approach limits the number of
youth who completed the survey. While students are strongly encouraged by school and
health officials to participate in the survey, no incentives or compensation are offered.
After receiving the necessary permissions, the survey is administered to students in 6th,
8th, 10th, and 12th grades in 39 of 41 school districts in Utah. Generally speaking, the
survey was offered to students during February and March. Given the length of the

survey, the time to complete the survey exceeded the time allowed for a single class.
Therefore, the survey was given over two different second hour class periods on
consecutive days. In 2017, the survey resulted in 54,853 total respondents statewide and
50,237 valid responses that would be included in the database. A total of 4,616
questionnaires were eliminated from the dataset by the sponsors of the survey. The
quality data that remained was then organized into 13 groups that corresponded with the
jurisdictional boundaries of the 13 local health departments that cover the 29 counties in
Utah. As a result, the data were made available to each local health department.
Before the administration of the survey, Bach Harrison, LLC, the contracted data
management company, reviewed current enrollment numbers and determined the
necessary threshold of students that needed to be sampled to provide a fair and adequate
representation of youth for each region. At the conclusion of the survey, the UDOH,
Bach Harrison, LLC, and the Utah Department of Substance Abuse and Mental Health
(UDSAMH) determined that each of the 39 participating school districts had received a
sufficient number of respondents for valid statistical analysis (UDHS, 2018). In
Summit County, the sampling techniques described above resulted in 1,244 responses
in 2017, 1,303, in 2015, 1,366 in 2013, and 1,367 in 2011 for students in 8th through
12th grades. In each of the listed years, the numbers listed above represented nearly
50% of the student body, meaning half of the students from the three school districts in
Summit County completed the survey.
The SHARP dataset used a non-probability voluntary sampling method to collect
the data from the PNA survey tool given the voluntary nature of the survey.

Nonprobability sampling methods are consistent with voluntary sampling methods where
participants self-select into a survey (Schweizer, Braun, & Milstone, 2016). The
advantages of a non-probability approach are convenience and cost of the sampling.
Unfortunately, this approach does not allow the original researchers to estimate the extent
to which the sample statistics differ from the general population (Maguire, Rosato, &
O’reilly, 2017). However, with the survey being voluntary and requiring parental consent
per the state rule, the approach to sampling was limited, and researchers must use what
methods are available and considered acceptable.
Data Management
An inter-local agreement between the UDOH and the Utah Association of Local
Health Departments allowed access to the SHARP dataset for this research. The
researcher made a formal written inquiry to the Summit County Health Officer requesting
permission to access the SHARP data in the raw format. The local Health Officer granted
permission and provided notification to the state contact responsible for the SHARP
dataset. The existing data use agreement between the Summit County Health Department
and the UDOH allowed Bach Harrison, LLC to release the requested dataset for research
purposes. The use and management of the data were consistent with the expectations
outlined in the existing data use agreement to ensure the data remained authentic and
uncompromised.
Justification for the Sample Size, Effect Size, Alpha Level, and Power Level
A power analysis using G*Power 3.1.9.2 helped determine the sample size and
power level for the statistical analyses portion of this research. The test family was z test,

the statistical test was a logistic regression, and the power analysis was A priori: Compute
required sample size. For the sample size and power analyses, the effect size was set at
0.2 and the alpha level was set at 0.05 to limit type 1 error and improve external validity
by increasing the opportunity to correctly reject the null hypothesis
(Creswell & Creswell, 2017). A power level of 80% was selected to reduce type 2 error
(Frankfort-Nachmias & Leon-Guerrero, 2015). The results of the power analysis
indicated a minimum sample size of 568 for this research. For this study, the sample size
for each year was 1,244 respondents (2017), 1,303 respondents (2015), 1,366 respondents
(2013), and 1,367 respondents (2011) with normal distribution. Each year provided a
larger sample size then what is required, thereby increasing the power above the initial
selection of 80%.
Instrumentation and Operationalization of Constructs
The PNA survey instrument was a tool used by UDOH and Utah Department of
Human Services (UDHS) to gather information about the different health and behavior
risks presented to youth within Utah’s communities. The PNA survey tool was offered to
youth in public schools in 6th, 8th, 10th, and 12th grade every 2 years and was voluntary.
The data collected by PNA survey was used by the UDOH and UDHS as the basis for the
creation of the SHARP survey project dataset (UDHS. 2018). The SHARP project was a
collaborative effort sponsored by the UDHS, Division of Substance Use and Mental
Health, Utah State Board of Education, and the UDOH. The findings of the survey from
the 39 different school districts were made available to all 13 local health departments in

the State of Utah as part of an executive agreement between the Utah Association of
Local Health Departments and the UDOH.
Variables provided by the SHARP dataset via the PNA survey tool were used to
operationalize the assessment of mental health, as it related to depression and suicide
ideation, in the youth attending public high school in Summit County. Four different
variables were used for this study: (a) grade, (b) zip code, (c) had seriously considered
suicide in the past 12 months, and (d) experienced a depressive episode in the last 12
months. Survey participants were provided predetermined lists for grade selection
(Grades 8, 10, or 12) and zip codes specific to residents in Summit County. In each
category, a selection was made from one of the predetermined answers that were specific
to Grades 8 through 12 and zip codes that were specific to Summit County, Utah.
Answers to the survey questions about depressive episodes and suicide ideation consisted
of “yes” or “no” options.
Variables regarding grade and zip code were identified as independent variables
for this research. Nominal scales of measurement were used to categorize the independent
variables. For purposes of comparison between the east and west sides of Summit
County, zip codes were combined into a dichotomous format (east or west) based on
location in relation to the separation created by U.S. highway 40. Nominal scales of
measurement were also used for the dependent variables of depressive episodes in the last
12 months and suicide ideation in the last 12 months.
Other variables related to ATOD risk, or individual social factors provided by the
PNA survey and the SHARP dataset were not considered for this research.

Data Analysis Plan
The Statistical Package for Social Science (SPSS) version 23 was used to perform
the analytical strategies suggested by Isaacs et al. (2014) and Read, Quinn, Berwick,
Fineberg, and Weinstein (1984) for the SHARP dataset. SPSS was used to run the
analyses for both the descriptive and inferential analyses. The descriptive statistics
included percentages, means, and graphs to provide a general characterization of the
secondary dataset (Thiese, 2014). Logistic regression was used to test hypothesis one and
two and examine the association between the binary dependent variables of suicide
ideation and depression and grade level in the youth of Summit County between the ages
of 14–18 from 2011 through 2017. A one-way analysis of variance (ANOVA) was used
to test hypothesis three and compare the frequencies of self-reported suicide ideation and
depression between zip codes on the east side and the west side from 2011 through 2017.
The SHARP dataset provided the necessary independent and dependent variables
for this research. Grade level was the independent variable and self-reported depression
was the dependent variable for research question one. Grade level was also the
independent variable for research question two with self-reported suicide ideation acting
as the dependent variable. For research question three, geographic location (east versus
west) was considered as the independent variable and suicide ideation and depression
were identified as the dependent variables.
Data Cleaning and Screening Procedures
The SHARP dataset contains multiple variables that are unnecessary for this
research. At the time the dataset was requested from Bach Harrison, LLC, specific

instructions were given as to what information was needed for this research. As a result,
Bach Harrison only delivered the variables of interest (grade, location, and survey results
for questions related to depressive episodes and suicide ideation). As a matter of privacy,
and to ensure compliance with protections described in the collaborative memorandum of
understanding with the individual school districts, the data management group handled
the data cleaning procedures. Upon delivery, Bach Harrison, LLC had made efforts to
clean and screen the data. The data management group handled the missing data, coding
errors, irregularities, and outliers before the dissemination of information. Missing
answers were coded using a “-9”. Multiple marks/ answers were coded as “-8”.
Irregularities and other errors were coded as “-4”. Prior to releasing the dataset for this
research, Bach Harrison, LLC analysts applied a raking ratio to the survey respondents.
The raking ratio respondent weighting method is a poststratification procedure for
adjusting sample weights in a survey to represent the known population characteristics of
each regional grouping (Deville, Särndal, & Sautory, 1993). This method of weighting
helped ensure the survey sample reflected the total population of Utah students by grade,
gender, and race/ethnicity (UDHS, 2018). Additionally, it allowed the data to accurately
represent the youth demographic of Summit County. Outliers missing more than 50% of
the survey questions were excluded from the provided dataset prior to delivery. The
initial efforts of Bach Harrison, LLC provided a great benefit to the research project and
helped expedite the data analysis portion of the study.

Once the dataset was received, it was entered into SPSS using methods described
by Wagner (2016) to ensure the data analyses were effective and correct. The results of
the analyses are found in chapter three.
Threats to Validity
In research, the term validity describes to what extent the research measures what
it intended to measure. With each type of research design, there are different and unique
threats to validity. Quasiexperimental research offers many advantages over true
experimental research (Kontopantelis et al., 2015). However, the lack of randomization
afforded by a quasiexperimental design presents challenges that threaten the internal and
external validity of the research. Although quasiexperimental research presents some
threats to validity, researchers can use various controls, such as omitting personal
information or unique identifiers, to overcome these concerns. However, these strategies
must be acknowledged and accounted for early during the research design process to
eliminate concerns of validity within the study (Schweizer et al., 2016). With multiple
threats to internal and external validity potentially influencing the findings of any
research, it is important that the individual methods used to increase the validity of the
study be discussed in full transparency.
Although the SHARP dataset has a long history of implementation and validation,
some common validity concerns related to secondary data still exist. As a secondary
dataset, there is potential for unknown errors in the collection of primary data and the
entry of data into the database (Johnston, 2017). The anonymous nature of the survey
makes it difficult to determine if the dataset provides an accurate representation of the

general population even with a large sample size. The voluntary aspect of the survey
presents potential bias through individuals with a vested interest in the survey topic being
more likely to participate in the survey when compared to the general population
(Creswell & Creswell, 2017). This bias could result in the answers provided being
skewed to one end of the spectrum depending on the subject of the survey and the interest
of those who participate (Shaw, Cross, Thomas, & Zubrick, 2015).
As with any self-reporting survey, the responses and the data generated from
those responses are dependent upon the honest and truthful answers of the youth taking
the survey. Short et al. (2009) reported that using self-reported measures introduces
exaggeration and over- commitment, which exposes research to concerns of validity and
bias. Additionally, self-reported surveys introduce a certain level of error based on
individual experiences. Although existing research shows that youth tend to answer
anonymous surveys honestly (Short et al., 2009), individual interpretation of life events
can vary greatly based on gender, age, and personal history. What one individual
perceives as a severe depressive episode might be interpreted as less severe by another
survey respondent. This difference in perception can result in different answers being
reported although the actual event shared many similarities as defined by a clinical
interpretation (Joffer, Jerdén, Öhman, & Flacking, 2016).
Further threats to validity arise from the time span of the dataset (2011–2017).
During this time, specific events that were unrelated to the CHA efforts for mental health
may have influenced the responses of individuals for better or worse. Additionally,

maturation in both the individual (physical/ natural) and his/her experience in completing
the survey could influence the answers provided over the course of the dataset timeframe.
As youth progress through puberty, their attitudes may change the provided response
(Short et al., 2009). Furthermore, there is the expectation that some youth will have
completed the survey multiple times during their high school years, which could also
change the outcome of the responses (Short et al., 2009).
While the use of a secondary dataset created through an anonymous, voluntary
survey, coupled with a quasiexperimental design present some threats to validity,
considerable efforts have been made to increase the validity of this research. Early efforts
by Bach Harrison, LLC to weight, clean, and refine the data through consistent processes
will improve the quality of the data and the validity of the research. Additionally, many
of the concerns noted are minimized with a large sample population taken over a longer
period of time (Frankfort-Nachmias & Leon-Guerrero, 2015; Glanz et al., 2015). With the
survey being an opt-in for youth, every student was given an equal opportunity to
participate. The opt-in aspect of the survey minimizes selection bias by researchers. The
anonymous nature of the survey presents a level of randomness that helps strengthen the
quality of the non-probability voluntary sample even when some bias may be present. As
a result of these efforts, a best faith effort has been made to increase validity with these
controls in place and other statistical controls applied during the analysis portion of the
research.

Ethical Procedures
One of the many benefits afforded by secondary data in research is that most of
the approvals and ethical considerations have been managed by the original research
group (Johnston, 2017). This assumption also applies to the SHARP dataset. As required
by Utah State Law, a completed and signed parental consent form was required before a
student could complete the PNA survey. Therefore, all of the respondents and the
answers provided in the dataset are compliant with state law as determined by the UDOH
and UDSAMH. By using a secondary dataset, the researcher never had direct contact
with any of the survey respondents nor participated in the administration of the survey.
This ensures the confidentiality and anonymity of the respondents being preserved. The
confidentiality of personal information is further enhanced by the purposeful exclusion of
unnecessary information, like gender, at the time the request for data was made. As a
result, the dataset provided by Bach Harrison, LLC included only relevant information to
this study, which limited the potential ethical concern of confidentiality.
The existing data user agreement provided a legally binding document that
required the dataset only be used for intended research purposes and that the information
not be distributed to anyone outside the researcher. The agreement further requires that
information is used only for the purpose defined in the agreement, and that any variation
or continuation of the research will require additional approvals. Furthermore, as outlined
in the data user agreement, it is required that the data be held in a safe, secure place to
eliminate the possibility of unpermitted dissemination. In an effort to honor the

agreement between agencies, the expectations of this agreement were upheld to the
highest degree.
The Walden University Institutional Review Board (IRB) provided formal review
and approval of this research on August 28, 2018. Once approval was received, the data
retrieval, data analysis, and interpretation portion of the research was able to commence.
Dataset Treatment Postanalysis
Per the existing data user agreement between the Utah Association of Local
Health Departments, UDOH, and the local school districts, the data used for this research
were deleted from the system once the research was completed and final approval was
received. This action not only satisfies the expectations of the data use agreement, but it
also represents responsible and ethical research using secondary data (Creswell &
Creswell, 2017).
Summary
The purpose of section two is to describe the research design and rationale, the
methodology of the research, and the potential concerns of validity for this study.
Additionally, the target population, sampling techniques, data analysis plan, data
management, and ethical considerations were described. Finally, the instrumentation and
operationalization of the variables are discussed in detail, which provides an
understanding of how the variables are measured and used for the research.
The SPSS program version 23 provided tools for the statistical analysis of the
SHARP dataset, which was provided by the PNA survey. All ethical considerations and
legal obligations regarding the survey were managed by Bach Harrison, LLC and the
dataset was acquired through appropriate channels between public health agencies in the

State of Utah. Additionally, evidence of approval from the Walden University IRB was
provided with the accompanying documentation.
Section two provides a descriptive foundation that supports the framework of the
study. Section three builds on the information provided in this section and describes the
statistical functions and theories that allow evidence-based assumptions to be made.
These conclusions are then applied to positive social change and recommendations are
made for how the results of this study can benefit local public health agencies.
Section 3: Presentation of the Results and Findings
The purpose of this study was to evaluate the effectiveness of CHA- driven
mental health interventions to reduce the self-reported frequencies of suicide ideation and
depression in the youth of affluent communities. This research, utilized mental health
data provided by the SHARP dataset for youth attending public school in Summit
County, Utah, an affluent area, for the calendar years 2011, 2013, 2015, and 2017. A
G*Power analysis confirmed the sample size was sufficient for this study, and the UDOH
and the UDSAMH confirmed the sample was representative of the local youth population
in Summit County, Utah. The dataset had been cleaned, screened, and coded by Bach-
Harrison, LLC prior to my receiving the data, which expedited the data analysis process.
All personal and sensitive information was removed from the dataset per the ‘Fair Use
Data Agreement’ to protect the anonymity. All survey responses in the dataset were
included in the analysis.
In this section, I present the results of the statistical analysis of the mental health
survey responses provided by the SHARP dataset. Section 3 concludes with a summary

of the findings from the data analysis performed. Section 4 provides an interpretation of
the results and the applicability of this research for creating social change.
Statistical Results
The statistics and inferential analysis results for RQ1 and RQ2 are presented first,
followed by the results for RQ3. First, the inferential analysis compared the individual
data from 2013, 2015, and 2017 to 2011. Then the cumulative data from 2013, 2015, and
2017 were compared to 2011. Each analysis was conducted in accordance with the data
analysis plan described in Section 2. The statistical analysis was performed using SPSS
version 23 under the direction provided by Wagner in his 2017 text on statistics for social
sciences.
Logistic Regression
The researcher used logistic regression for RQ1 to determine the correlation
between the frequencies of self-reported depression in 8th, 10th, and 12th grade students
when comparing the frequency of responses from postCHA-driven mental health
interventions to the frequency of responses from preCHA-driven mental health
interventions in the youth attending public high school in Summit County, Utah.
Logistic regression was also used for RQ2 to determine the correlation between
the frequencies of self-reported suicide ideation in 8th, 10th, and 12th grade students
when comparing the frequency of responses from postCHA-driven mental health
interventions to the frequency of responses from preCHA-driven mental health
interventions in the youth attending public high school in Summit County, Utah.

This analytical approach determined the strength of the relationship between the
self-reported presence- absence of depression and suicide ideation in the surveyed
population, grades 8, 10, and 12, where CHA-driven mental health interventions were
implemented. As stated by Kontopantelis et al. (2015), the use of logistic regression is
acceptable for determining the strength of the relationship in a quasiexperimental design
using two or more independent variables. For this analysis, 2011 was designated as the
quasicontrol and compared to survey results from 2013, 2015, and 2017, both
individually and collectively.
The number of survey responses for the logistic regression are presented in table
one. The survey respondents are separated by grade and by year to provide evidence of
adequate representation for each grade sampled. In total, 42% (n = 1271) of the survey
respondents were in 8th grade, 33% (n = 982) were in 10th grade, and 24% (n = 625)
were in 12th grade.
Table 1
Frequency of Survey Responses by Grade and Year for Self-reported Depression and
Suicide Ideation
Grade Level Survey Responses by Year
2011
n=453
2013
n=967
2015
n=928
2017 n=625 Total
n=2973
Selfreported
depression
during the
last 12
months
8th Grade
%
10th Grade %
196 (21)
43.2 (10.7)
145 (22)
32.0 (15.2)
322 (59)
33.3 (18.3)
361 (68)
37.3 (18.8)
390 (87)
42.0 (22.3)
318 (69)
34.2 (21.7)
363 (58)
58.1 (16.0)
158 (34)
25.3 (21.5)
1271 (225)
42.8 (17.7)
982 (193)
33.0 (19.7)
12th Grade 112 (12) 284 (45) 220 (40) 104 (26) 720 (123)
% 24.7 (10.7) 29.4 (15.8) 23.7 (18.2) 16.6 (25.0) 24.2 (17.1)

Selfreported
suicide
ideation
during the
last 12
months
8th Grade
%
10th Grade %
196 (15)
43.2 (7.7)
145 (18)
32.0 (12.4)
322 (36)
33.3
361 (34)
37.3
390 (49)
42.0 (12.6)
318 (44)
34.2 (13.8)
363 (46)
58.1 (12.7)
158 (30)
25.3 (19.0)
1271 (146)
42.8 (11.5)
982 (126)
33.0 (12.8)
12th Grade 112 (10) 284 (26) 220 (31) 104 (16) 720 (83)
% 24.7 (8.9) 29.4 23.7 (14.1) 104 (15.4) 24.2 (11.5)
Note: (*) indicates the number of positive responses for that question compared to the
overall number of responses.
The number of survey responses provide evidence that the sample size met the
requirements established by the G*Power analysis. Figures 1–4 provide visual
representation of the answers for depression and suicide ideation. The figures are
separated by grade with categories for “yes” and “no” provided for each survey response.
Additionally, the figures provided help to show whether an increase in the number of
self-reported mental health survey responses occurred and how each grade was impacted
by depression and suicide ideation. A brief assessment of the figures indicated a large
increase in the number of students self-reporting depression and suicide ideation
following the implementation of “Hope Squad” and “QPR” in 2012. There is a reduction
in the number of positive survey responses from 2015 to 2017. However, the frequencies
of self-reported depression and suicide remain proportionately similar to previous survey
years. The increase in self-reported depression and suicide ideation could be attributed to
extrinsic factors that influenced survey responses, such as the method of delivery, all of
which are discussed in section four.
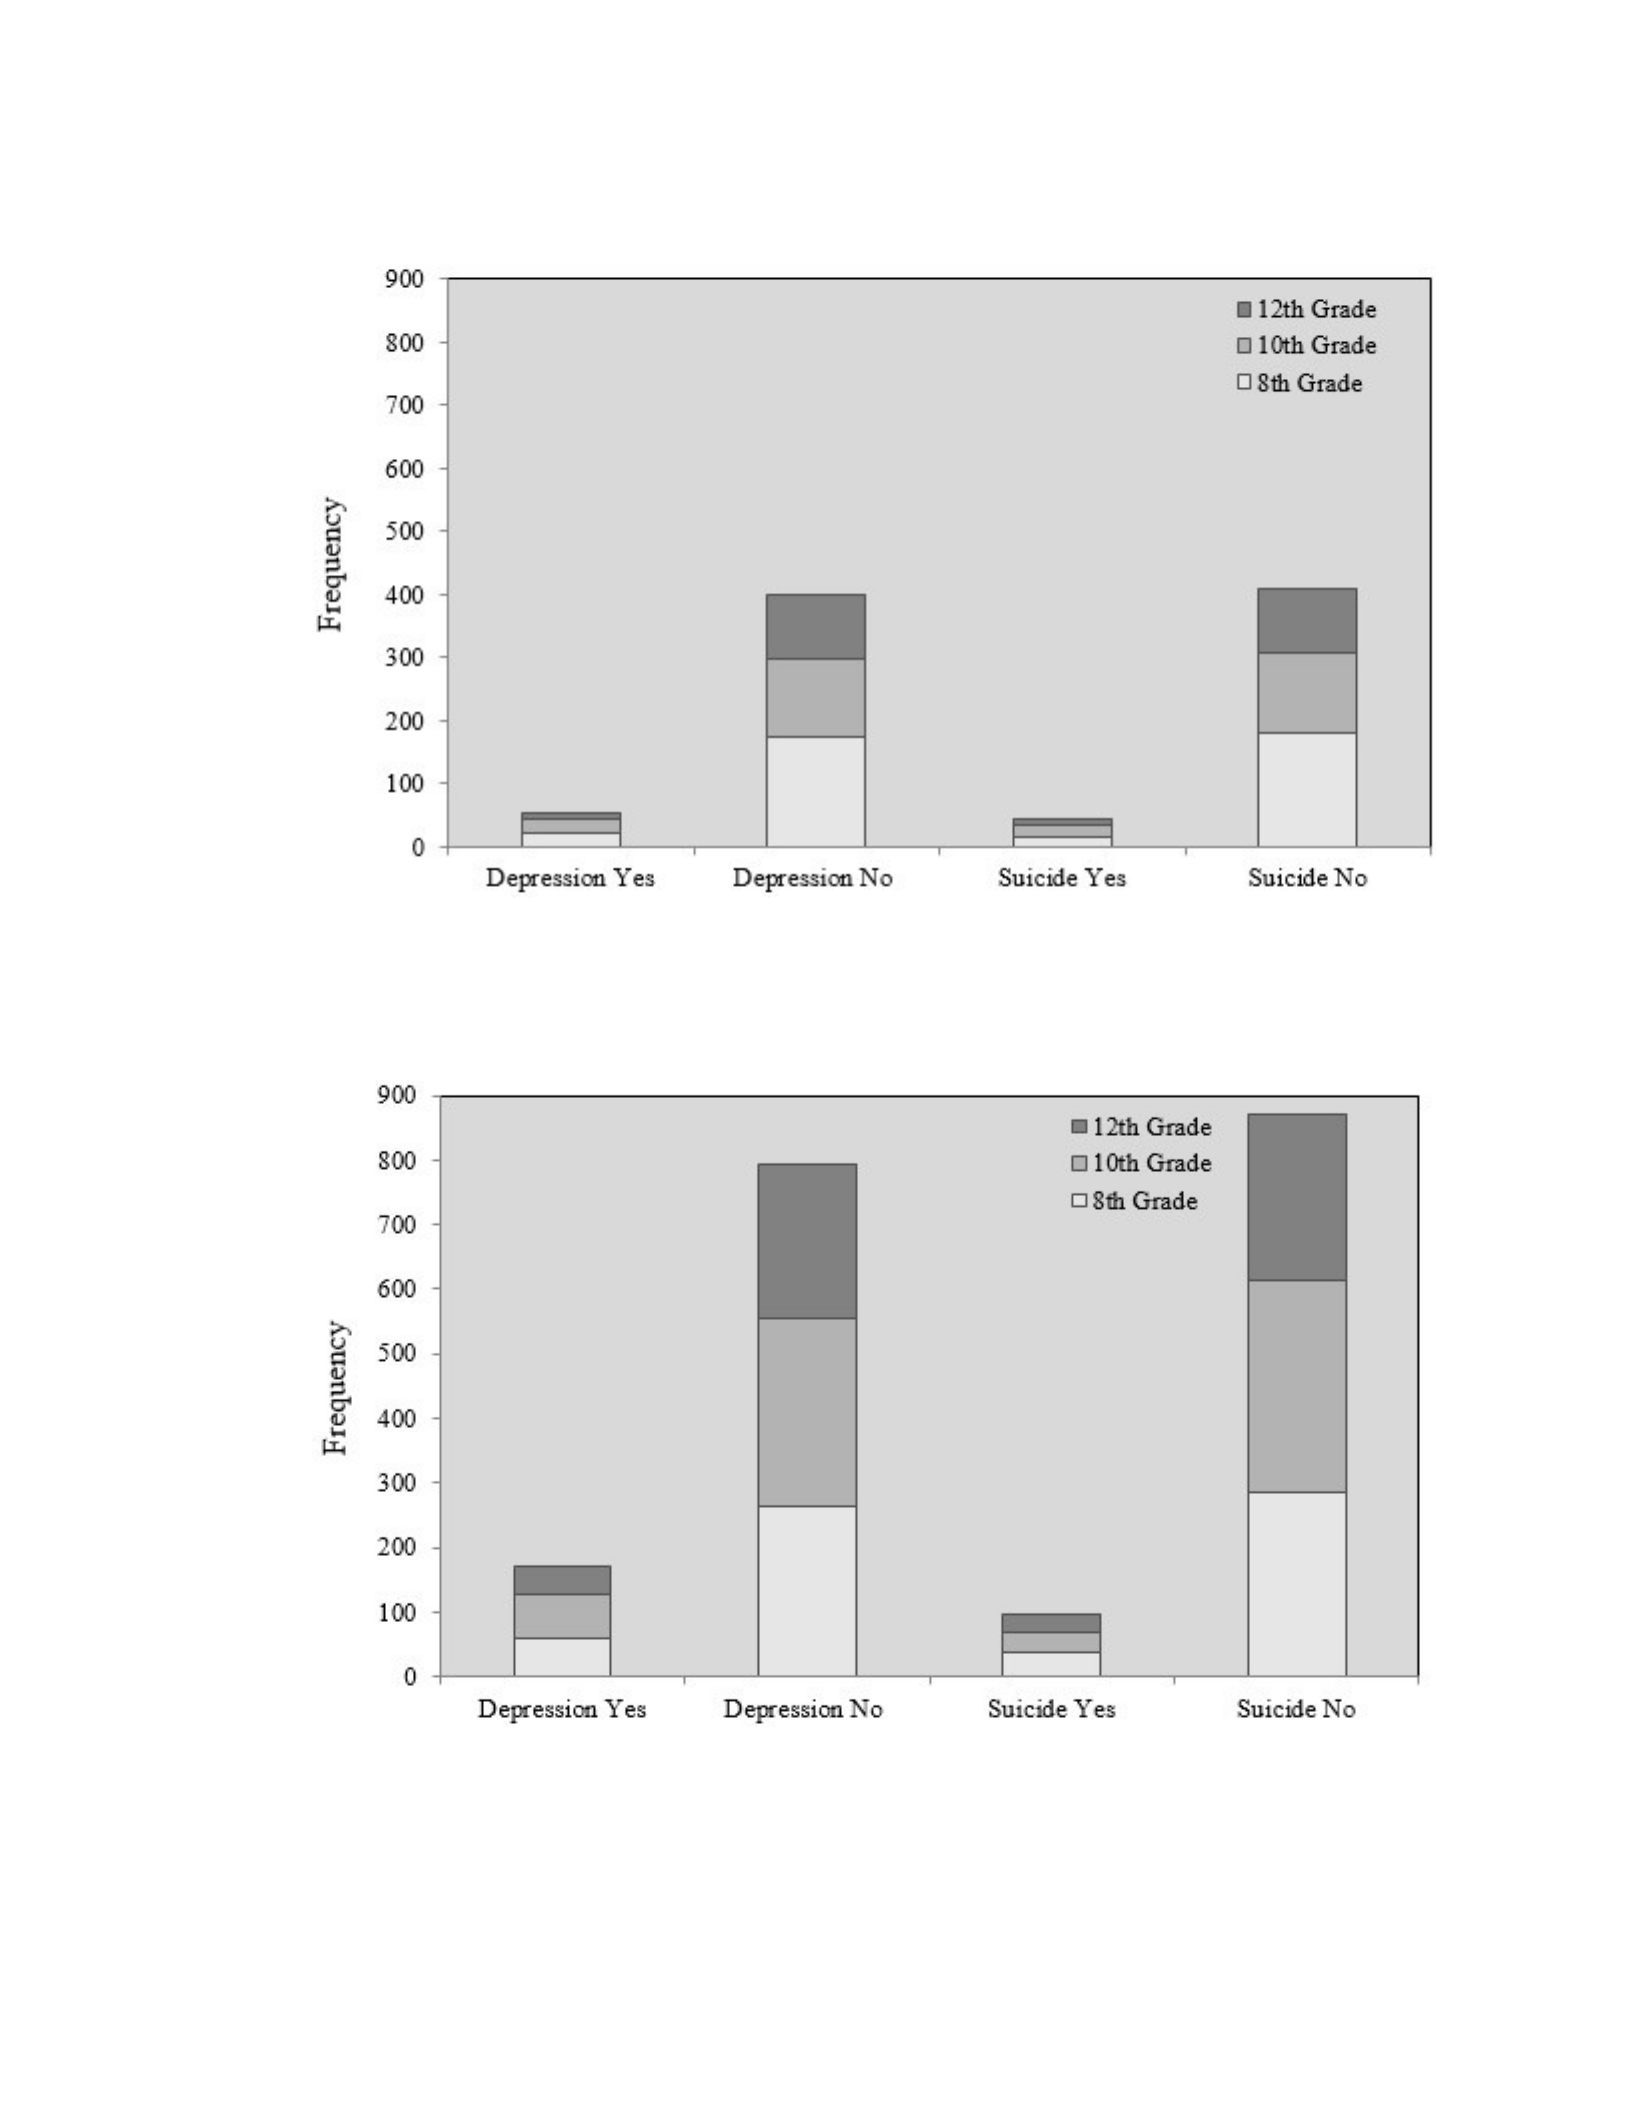
Figure 1. Self-reported depression and suicide by grade during the 2011 school year.
Figure 2. Self-reported depression and suicide by grade during the 2013 school year.
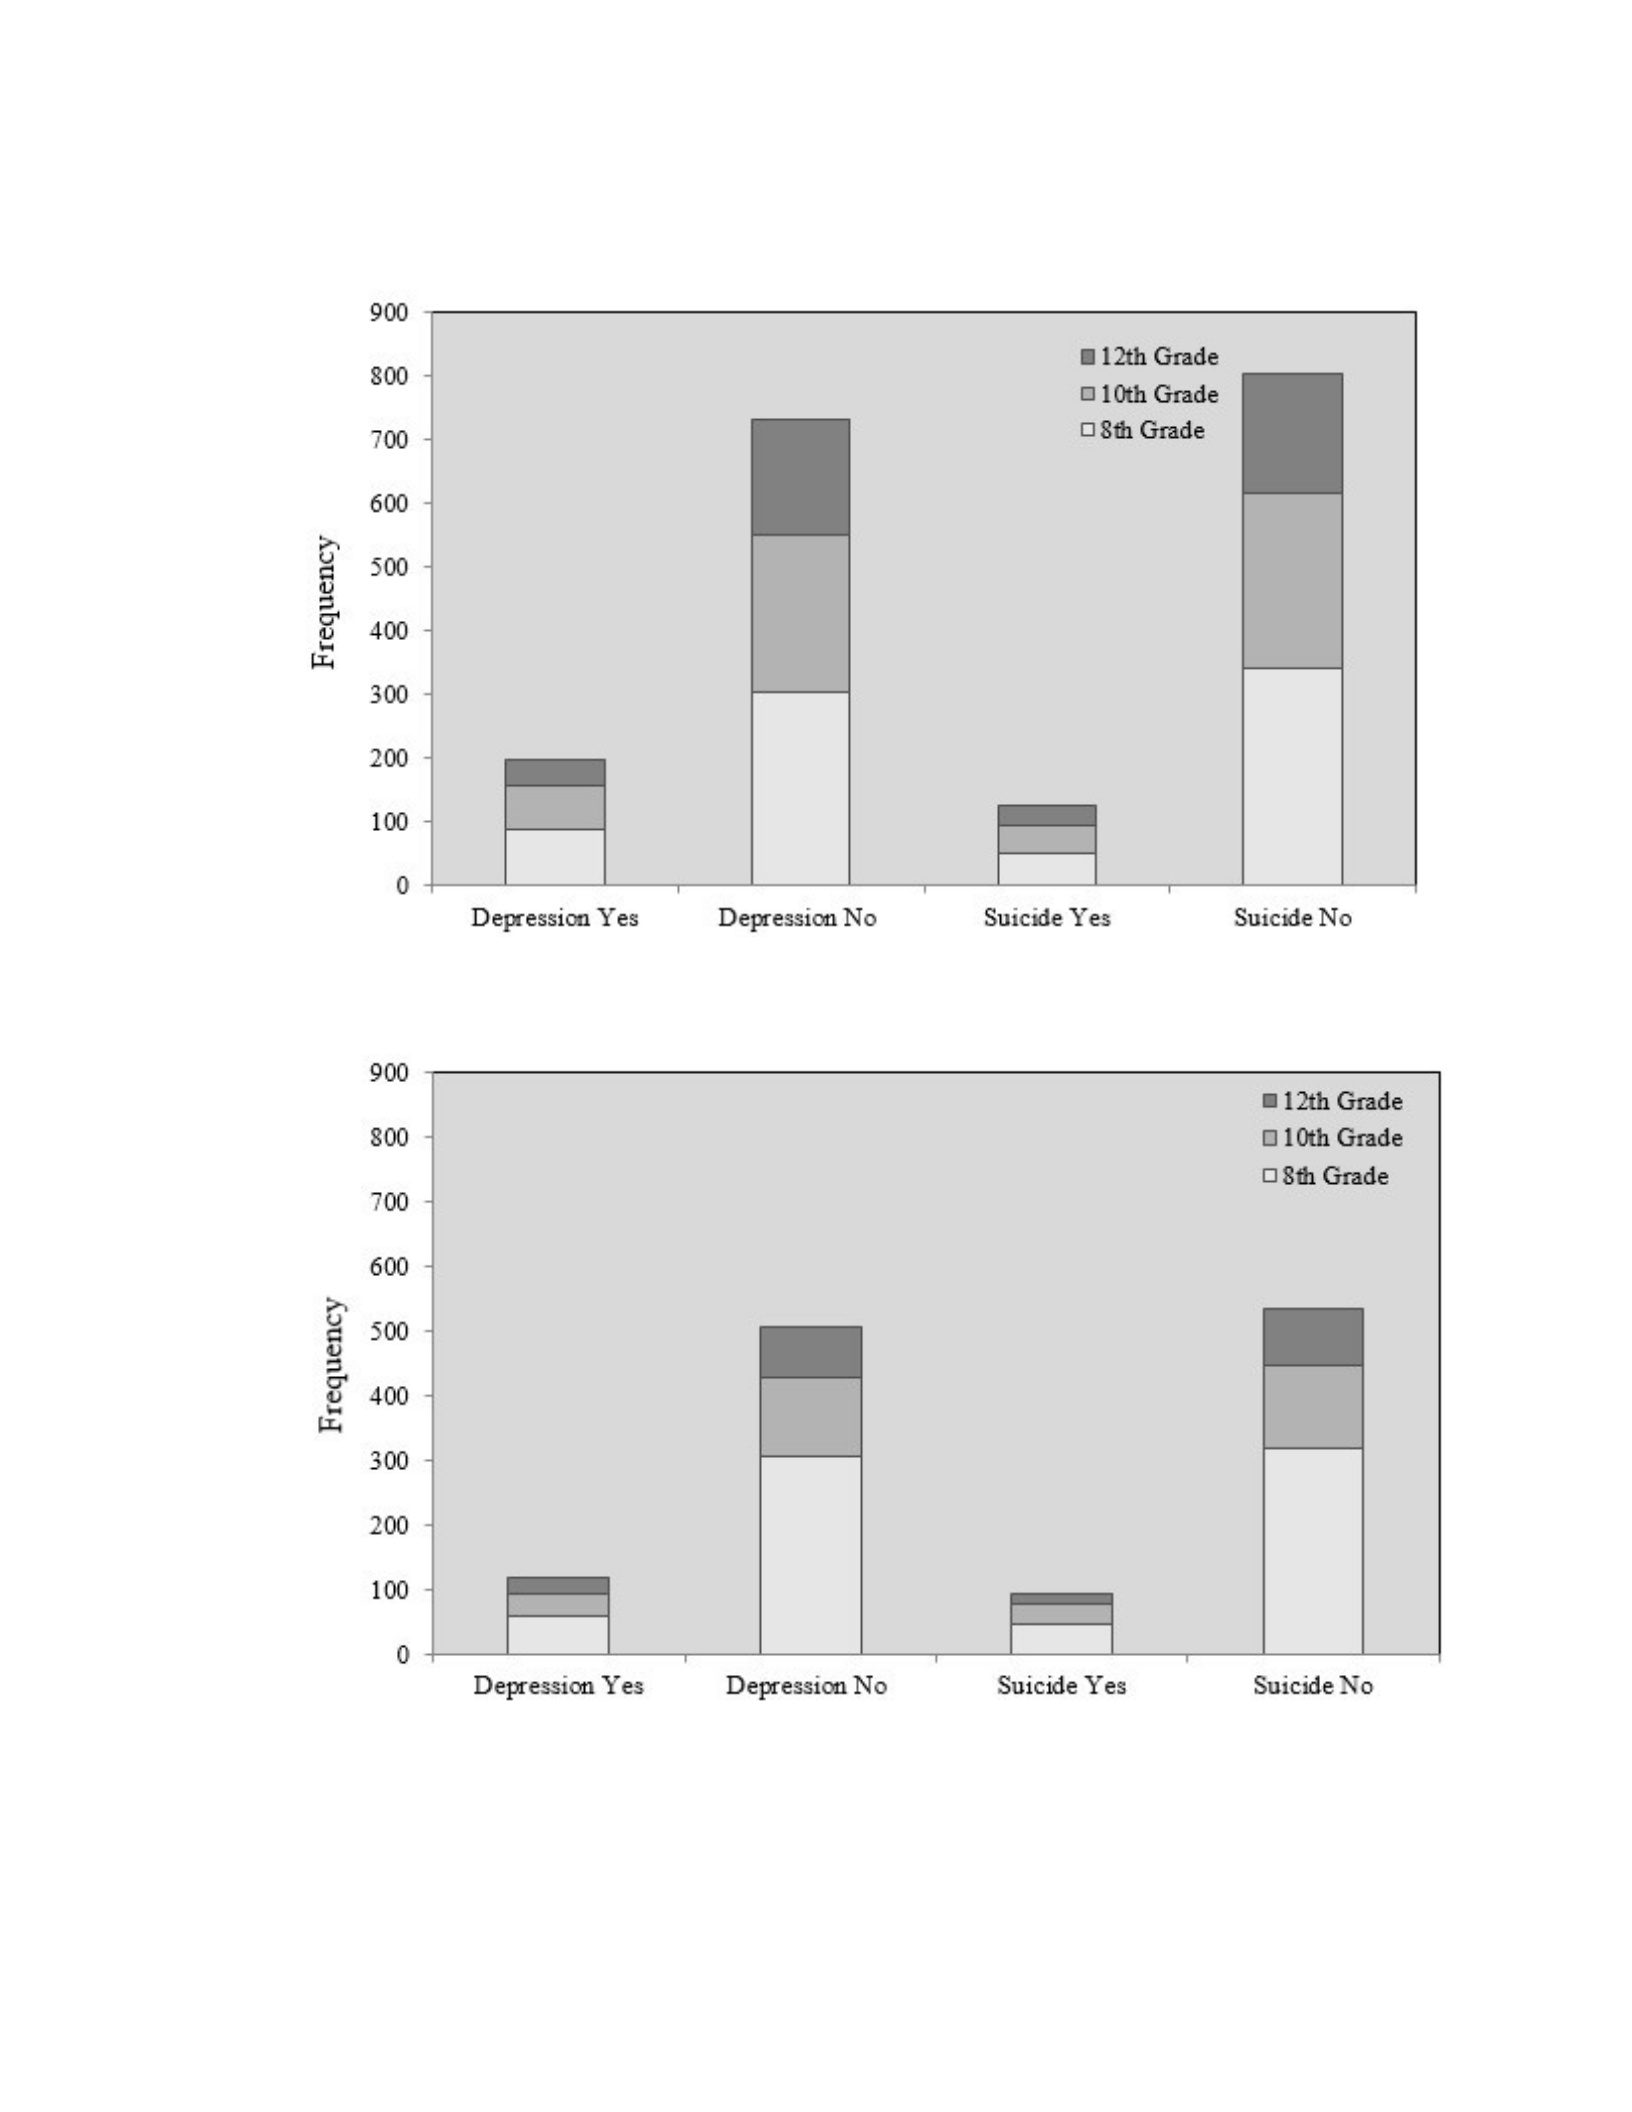
Figure 3. Self-reported depression and suicide by grade during the 2015 school year.
Figure 4. Self-reported depression and suicide by grade during the 2017 school year.

This analysis provided a comparison of the survey results of 2011 to 2013, 2015,
and 2017 individually. From the statistical analysis it was determined that the differences
in the frequencies of self-reported depression in the target population were not
statistically significant between grades postintervention, both individually and
cumulatively. The analysis of suicide ideation provided the same results.
Tables 2 through 5 provide the outputs for the self-reported depression survey
results used to answer research question one. The results of the logistic regression
indicated that while students in 8th, 10th, and 12th grades attending public high school in
Summit County, Utah reported feelings of depression, the differences between grades
from 2011 to subsequent years were not statistically significant. In 2017, the reports by
8th of feeling depressed approached significance (p= .060) when compared to survey
responses from the 2011 survey. However, these results fell short of the predetermined
criteria and cannot be considered significant. Therefore, null hypothesis for RQ1 that
there is no correlation between the frequencies of self-reported depression, by grade level,
when comparing the frequency of responses from postCHA-driven mental health
interventions to the frequency of responses from preCHA-driven mental health
interventions in the youth attending public high school in Summit County, Utah cannot be
rejected.
Table 2
Students Self-reporting Feeling Depressed During the 2013 School Year by Grade when
Compared to 2011 Survey Responses
Variable B S.E. Wald df Sig. Exp(B)
Step 1a 8th Grade -.175 .217 .651 1 .420 .839
10th Grade -.209 .211 .982 1 .322 .811
12th Grade -1.285 .255 2.315 1 .198 .277
a. Variable(s) entered on step 1: 8th Grade, 10th Grade, 12th Grade
Table 3
Students Self-reporting Feeling Depressed During the 2015 School Year by Grade when
Compared to 2011 Survey Responses
Variable B S.E. Wald df Sig. Exp(B)
Step 1a 8th Grade -.241 .213 1.281 1 .258 .786 10th Grade -.239 .221 1.170 1 .279 .787
12th Grade -.102 .253 1.423 1 .507 .359
a. Variable(s) entered on step 1: 8th grade, 10th grade, 12th grade
Table 4
Students Self-reporting Feeling Depressed During the 2017 School Year by Grade when
Compared to 2011 Survey Responses
Variable B S.E. Wald df Sig. Exp(B)
Step 1a 8th Grade .509 .271 3.545 1 .060 1.664
10th Grade .106 .299 .126 1 .722 1.112
12th Grade .587 .331 1.225 1 .238 .171
a. Variable(s) entered on step 1: 8th grade, 10th grade, 12th grade
Table 5
Students Self-reporting Feeling Depressed During the 2013, 2015, and 2017 School
Years by Grade when Compared to 2011 Survey Responses
Variable B S.E. Wald df Sig. Exp(B)
Step 1a 8th Grade -.071 .131 .295 1 .587 .931
10th Grade -.172 .136 1.596 1 .206 .842
12th Grade -1.272 .156 6.130 1 .652 .280

a. Variable(s) entered on step 1: 8th grade, 10th grade, 12th grade
The statistical results for RQ2 are provided in tables 6 through 9. The findings of
this research indicated the same results for research question two as found in question
one. The results of the logistic regression indicated that while students in 8th, 10th, and
12th grades attending public high school in Summit County, Utah did report feelings of
suicide ideation, the differences between grades from 2011 to subsequent years were not
statistically significant. In 2017, the reports by 10th graders of suicide ideation
approached significance (p= .064) when compared to survey responses from the 2011.
However, these results fell short of the predetermined criteria and cannot be considered
significant either. Therefore, the null hypothesis for research question two that there is no
correlation between the frequencies of self-reported suicide ideation, by grade level,
when comparing the frequency of responses from postCHA-driven mental health
interventions to the frequency of responses from preCHA-driven mental health
interventions in the youth attending public high school in Summit County, Utah cannot be
rejected.
Table 6
Students Self-reporting Suicide Ideation During 2013 School Year by Grade when
Compared to 2011 Survey Responses
Variable B S.E. Wald df Sig. Exp(B)
Step 1a 8th Grade -.265 .274 .938 1 .333 .767
10th Grade -.106 .275 .150 1 .699 .899 12th Grade -1.966 .327 3.202
1 .551 .140
a. Variable(s) entered on step 1: 8th Grade, 10th Grade, 12th Grade
Table 7

Students Self-reporting Suicide Ideation During 2015 School Year by Grade when
Compared to 2011 Survey Responses
S.E. Wald df Sig.
Step 1a 8th Grade -.160 .265 .365 1 .546 .852 10th Grade
-.445 .265 2.819 1 .093 .641
12th Grade -.266 .306 2.927 1 .099 .224
a. Variable(s) entered on step 1: 8th grade, 10th grade, 12th grade
Table 8
Students Self-reporting Suicide Ideation During 2017 School Year by Grade when
Compared to 2011 Survey Responses
Variable B S.E. Wald df Sig. Exp(B)
Step 1a 8th Grade .168 .321 .275 1 .600 1.184
10th Grade -.370 .344 1.162 1 .281 .690
12th Grade -.772 .379 2.377 1 .524 .206
a. Variable(s) entered on step 1: 8th grade, 10th grade, 12th grade
Table 9
Students Self-reporting Suicide Ideation During 2013, 2015, and 2017 School Years by
Grade when Compared to 2011 Survey Responses
S.E
. Wald df Sig.
Step 1a 8th Grade -.183 .161 1.293 1 .256 .833
10th Grade -.319 .166 3.709 1 .054 .727 12th Grade -1.632 .190 4.153
1 .188 .195
a. Variable(s) entered on step 1: 8th grade, 10th grade, 12th grade
Variable B Exp(B)
Variable B Exp(B)

One-way ANOVA
The one-way ANOVA was used to evaluate RQ3 and determine if there is a
statistically significant difference between the frequencies of depressive episodes and
suicide ideation in the youth (ages 14-18) of eastern Summit County and the youth (ages
14-18) of western Summit County when CHA-driven mental health interventions are
similarly applied. According to Frankfort-Nachmias and Leon-Guerrero (2015), the
oneway ANOVA is an effective tool to determine statistical significance between the
means of two or more independent groups, making it an appropriate statistical test to
answer research question two. The one-way ANOVA analysis compared the survey
results of 2011 to 2013, 2015, and 2017 individually. Next, survey results from 2011
were compared to the cumulative results from 2013, 2015, and 2017. The results of this
analysis are provided below.
The number of regional survey responses by year used for the one-way ANOVA
are provided in table 12. The frequency of survey responses indicates that the sample size
met the parameters established by the G*power test. Additionally, table 12 provides the
number of survey responses for each year by region. Some variation in the number of
responses from year to year is present as indicated by table 12. Based on the sample size,
this did not impact the results of this study.
Table 10
Frequency of Survey Responses by Geographic Region in Summit County and Year for
Self-reported Depression and Suicide Ideation
Regional Survey Responses by School Year
2011 2013 2015 2017 Total

n=453 n=967 n=928 n=625 n=2973
Selfreported
depression
during the
last 12
months
West Summit
County
%
East Summit
County
%
285 (33)
63.0 (11.6)
168 (22)
37.0
(13.1)
590 (105)
61.0 (17.8)
377 (67)
39.0 (17.8)
632 (118)
68.1 (18.7)
296 (78)
31.9 (26.4)
335 (66)
53.6 (19.7)
290 (52)
46.4 (17.9)
1842 (322)
62.0 (17.5)
1131 (219)
38.0 (19.4)
Selfreported
suicide
ideation
during the
last 12
months
West Summit
County
%
East Summit
County
%
285 (27)
63.0 (9.5)
168 (16)
37.0 (9.5)
590 (65)
61.0 (11.0)
377 (31)
39.0 (8.2)
632 (86)
68.1 (13.6)
296 (38)
31.9 (12.8)
335 (57)
53.6 (17.0)
290 (35)
46.4 (12.1)
1842 (235)
62.0 (12.8)
1131 (120)
38.0 (10.6)
Note: (*) indicates the number of positive responses for that question compared to the overall number of
responses.
The results of the inferential analysis are shown in tables 11–15. The analysis
showed that while there were differences in frequencies of self-reported depression and
suicide ideation among students from eastern and western Summit County, those
differences were not statistically significant. This interpretation is supported by F values
at or near 1.0 and values of p > 0.05. This interpretation is shared across all years of the
survey responses. Therefore, the null hypothesis of RQ3 that there is no correlation in
frequencies of self-reported suicide ideation and depressive episodes between the youth
(ages 14-18) of eastern Summit County and the youth (ages 14-18) of western Summit
County when CHA-driven mental health interventions are similarly applied cannot be
rejected.
Table 11

Students by Region in Summit County Self-reporting Feeling Depressed and Suicide
Ideation for 2011 School Year
Sum of
Squares df Mean
Square F Sig.
Self-reported feeling
depressed in the last 12
months
Between
Groups
Within
Groups
.068
39.658
1
451
.068
.088
.774
.379
Total 39.726 452
Self-reported suicide
ideation in the last 12
months
Between
Groups
Within
Groups
.120
66.623
1
623
.049
.075
.653
.420
Total 66.744 624
Table 12
Students by Region in Summit County Self-reporting Feeling Depressed and Suicide
Ideation for 2013 School Year
Sum of
Squares df Mean
Square F Sig.
Self-reported feeling
depressed in the last 12
months
Between Groups
Within
Groups
.165
134.696
1 965
.165
.140
1.181
.277
Total 134.860 966
Self-reported suicide
ideation in the last 12
months
Between Groups
Within
Groups
.054
78.297
1 965 .054
.081
.667
.414
Total 78.352 966
Table 13

Students by Region in Summit County Self-reporting Feeling Depressed and Suicide
Ideation for 2015 School Year
Sum of
Squares df Mean
Square F Sig.
Self-reported feeling
depressed in the last 12
months
Between
Groups
Within
Groups
.057
151.042
1 926
.057
.163
.351
.554
Total 151.099 927
Self-reported suicide
ideation in the last 12
months
Between
Groups
Within
Groups
.014
102.235
1 926
.014
.110
.127
.722
Total 102.249 927
Table 14
Students by Region in Summit County Self-reporting Feeling Depressed and Suicide
Ideation for 2017 School Year
Sum of
Squares df Mean
Square F Sig.
Self-reported feeling
depressed in the last
12 months
Between Groups
Within
Groups
.113
87.910
1 623
.113
.141
.798
.372
Total 88.022 624
Self-reported suicide
ideation in the last 12
months
Between Groups
Within
Groups
.120
66.623
1 623 .120
.107
1.123
.290
Total 66.744 624
Table 15
Students by Region in Summit County Self-reporting Feeling Depressed and Suicide
Ideation for 2013, 2015, and 2017 School Years

Sum of
Squares df Mean
Square F Sig.
Self-reported feeling
depressed in the last 12
months
Between
Groups
Within Groups
.008
361.210
1
2518
.008
.143
.057
.811
Total 361.219 2519
Self-reported suicide
ideation in the last 12
months
Between
Groups
Within Groups
.000
244.184
1
2518
.000
.097
.003
.954
Total 244.184 2519
Summary
This section presents the results provided by the analytical strategies used to
analyze research questions one, two, and three of this study. Logistic regression was
used to assess the relationships between grade level and depression and suicide ideation
in youth attending 8th, 10th, and 12th grades in public high school between the years
2011 to 2017. Comparative analysis of data from 2011 was provided individually for
each subsequent year (2013, 2015, and 2017) as well as cumulatively (all cases from
2013– 2017). This approach provided an opportunity to evaluate the effectiveness of the
CHAdriven interventions for each year the survey was given and for the time period
selected. Collectively, the logistic regression analyses showed that the differences in the
frequencies self-reported depression and suicide ideation between the 8th, 10th, and 12th
grades grade students from 2011 to 2017 were not statistically significant. These
findings were mirrored in the year-to-year analysis as well. Therefore, the null
hypothesis could not be rejected.

A one-way ANOVA was used to evaluate the variations in depression and
suicide ideation between high school aged youth geographically separated by east and
west in Summit County, Utah. To remain consistent with the analytical approach used
for RQ1, the one-way ANOVA analysis was completed for 2011 and each year the
survey was administered thereafter (2013, 2015, and 2017) and also included a
cumulative test that compared all cases from 2013–2017 to 2011. The results of the one-
way ANOVA test showed that the differences in frequencies of self-reported depression
and suicide ideation between eastern and western Summit County were not statistically
significant. Therefore, the null hypothesis could not be rejected.
Section four, the final section of this document, interprets the findings of section
three. Section four references additional literature and provides a case for how these
findings, although statistically insignificant, should be used to create social change and
drive public health efforts to address mental health in the youth of all communities.
Furthermore, section four provides a theory of how survey responses may have been
influenced and suggestions for future research on the topic of mental health in affluent
communities.
Section 4: Application to Professional Practice and Implications for Social Change
Introduction
The mental health of youth in America is rapidly deteriorating across all
socioeconomic classes. Leading public health agencies (CDC, 2017; UN, n.d.; WHO,
2014), recent publications (Lê-Scherban et al., 2016; Schaefer et al., 2017), and textbooks

on the subject (Levine, 2008) have identified mental health, especially of youth, as a
major public health concern. Local public health agencies have assumed the bulk of
mental health intervention activities and have employed traditional public health
strategies, like the CHA, to help address mental health at the local level. Although these
efforts have provided some success (Henderson et al., 2013), the majority of research
supporting a conventional approach to mental health interventions has focused on
children and youth from lower socioeconomic classes. According to Bor et al. (2014)
and Fazel et al. (2012), these traditional public health efforts have proven effective in
dealing with public health concerns for young people of low socioeconomic status.
However, there is no evidence supporting the effectiveness of using established public
health efforts to address the mental health of youth in affluent communities.
This section includes a formal interpretation of the findings and discusses the
limitations of this study while providing suggestions for future research on the topic of
mental health in the youth of affluent communities. Most importantly, this section
includes the social and public health implications of this research and how it can be used
to assist local public health agencies struggling to improve the mental health status of
youth in affluent communities. These findings provide powerful evidence of how
CHAdriven interventions can improve mental health outcomes through increased
reporting and a heightened awareness around depression and suicide ideation in the
youth of affluent communities. Finally, this section concludes with a forecast of public

health’s important role in framing the future of mental health through the stewardship of
evidence-based programs that merge science with social and political will.
The purpose of this quantitative study was to investigate the effectiveness of a
CHA-driven intervention, a traditional public health approach, to reduce the self-
reported frequencies of mental health status among the youth of affluent communities.
This research provided evidence for depression and suicide ideation in the youth of
affluent communities attending public high school where CHA- driven mental health
interventions had been applied. Secondary data supplied by the SHARP dataset provided
self-reported depression and suicide ideation information on the youth of Summit
County, Utah for years 2011, 2013, 2015, and 2017. The current study evaluated
selfreported depression and suicide ideation in youth by grade level (8th, 10th, and 12th
grades) and by geographic region in Summit County before and after CHA-driven
interventions were implemented. In doing so, these findings provide local public health
agencies working in affluent communities with information that could be used to guide
their efforts.
Logistic regression was used to evaluate if the differences in self-reported
depression between grades from 2011 to subsequent years were statistically significant.
The analysis was then run again to determine the differences between suicide ideation
by grades for the same period. Additionally, a one-way ANOVA was used to determine
if the differences in self-reported depression and suicide ideation between eastern and
western Summit County pre- and postCHA-driven mental health interventions were

statistically significant during the selected time frames. All three analyses indicated that
the differences in self-reported depression and suicide ideation between grades and
geographic locations from 2011 compared to years 2013, 2015, and 2017, both
individually and collectively, were not statistically significant (p> 0.05). These findings
indicated that while individual youth are experiencing depression and suicide ideation at
each grade level and in each year and region, the differences between for these
conditions were not statistically significant. However, this research is still valuable for
the public health professional working to create social change around mental health in
affluent communities.
Interpretation of Findings
Statistical analyses determined that while there are students in Summit County
suffering from depression and suicide ideation, the variation between grades (8th, 10th,
and 12th grades) and geographic location were not statistically significant. As a result,
the null hypothesis for all three research questions could not be rejected. These findings
are in line with the findings of previous research presented section one. Unfortunately, all
youth, despite socioeconomic position, geographic location, and grade level, are at risk
for challenges related to mental health. However, this study was unable to determine if
grade and location were predicting variables for mental health outcomes.
Suicide and Depression
According to Joffer et al. (2016), self-reported surveys completed by youth create
challenges for researchers trying to compare self-perceived diagnoses to the actual

clinical diagnoses. Individual perceptions, interpretations, and experiences can all bias
how a survey respondent answers a single question. Additionally, self-reported disease
rates can increase when individuals are made aware of the symptoms, risks, or presence
of a disease within their community (Pursey et al., 2014). The number of students
selfreporting depression and suicide ideation increased in the target population from
2011, preCHA driven intervention, to 2015, postCHA-driven intervention. A small
decrease was noted between 2015 and 2017, but the proportion of positive responses
remained similar during this period given the number of overall responses. This suggests
that the CHA-driven interventions might not have been successful in reducing the number
of cases of depression and suicide ideation. Another plausible interpretation is that the
CHA-interventions increased awareness of these conditions among the youth, helping
them identify their feelings and emotions associated with depression and suicide ideation.
As a result, the reported number of cases postCHA-driven interventions might be more
representative of the problem than what was reported preintervention in 2011.
Grade Level
The results of the logistic regression provided evidence that there was no
association between the presence of depression and suicide ideation and grade level in the
youth of Summit County based on preintervention survey responses when compared to
postintervention survey responses. These findings were consistent for individual survey
years and collective survey years. In 2017, 8th grade students reported levels of
depression that approached levels of significance (p= 0.60) when compared to response

frequencies from the 2011 survey. This could indicate the problem is more prevalent
among the newer student body just entering high school. If that is so, there could be a
continued increase in the number of self-reported cases of depression among the younger
students over the next few survey cycles. Entering high school can be a difficult and
frightening event, which may lead to a higher rate of depression among 8th graders as
they struggle to deal with the anxieties that accompany the transition from middle to high
school.
Collectively, students in the 10th grade approached levels of significance (p=
0.64) for suicide ideation when compared to the response frequencies from the 2011
survey. Similar results were found in 10th graders during the 2015 school year (p=
.093). This is of interest given that the 10th graders reporting in 2015 would have been
given an opportunity to complete the survey in 2017, but an increase in positive survey
responses was not found. Although both results were not significant based on the
parameters established for this research, these findings help raise awareness about the
declining mental health of 10th graders in affluent communities. Additionally, these
results can help local public health agencies further investigate what might be different
in 10th graders compared to other grades in affluent communities.
Geographic Location
The one-way ANOVA provided evidence that helped determine the difference of
self-reported depression and suicide ideation between the youth of eastern and western
Summit County was not significant. With f-values near or below one (f = 0.003- 1.123)

and p values well above 0.05, it was determined that youth in affluent communities, are
at risk for poor mental health outcomes. These results support the findings of Bor et al.
(2014), Elgar et al. (2016), and Luthar and Barkin (2012) that the youth of affluent
communities are at risk of poor mental health outcomes. These findings thus provide
local public health agencies with an understanding that, despite individual
circumstances, mental health continues to be non-selective in who it affects. Wealth and
resources do not provide protections to the children of affluent communities.
Applicability to Diffusion of Innovation Theory
The theoretical framework of the DOI theory can be used to evaluate how public
health messaging disseminates throughout a community. The speed at which the
messaging moves is dependent upon perceived value and the individual stages of
adoption (Glanz et al., 2015). The stages of adoption are categorized into five groups
labeled according to the time when the message was adopted. The progression through
these five groups is what determines the effectiveness of the intervention messaging
(Greenberg, 2006).
According to the DOI theory, innovators and early adopters are the first group to
receive the messaging, but are the fewest in number, making up 15% of the target
population. The early majority and late majority adopters comprise 68% of the target
population. The remaining 16% are labeled as laggards and are the last group to adopt
the messaging, if at all.

The messaging around mental health was initiated post-2011 when the
CHAdriven intervention strategies were implemented. Although the messaging focused
on mental health and discovering ways to manage depression and suicide, it appears these
efforts worked to increase awareness. As individual youth became aware of mental health
definitions, they were willing to participate in the effort to improve mental health and
report individual circumstances by voluntarily taking the SHARP survey. This influx of
new survey responses, as shown by the general increase in survey responses from 2011 to
2017, mirrors the DOI theory framework and the progression through the different stages
of message adoption by the target population. While the intervention efforts did not have
the intended outcomes, the messaging raised awareness and increased the number of
“yes” survey responses each year. Therefore, based on the framework of the DOI theory,
the trend of increased survey responses should continue in the coming survey years as the
late adopters and laggards, who previously opted out of survey participation, choose to
participate in the 2019 SHARP survey. As a result, future researchers can expect an even
more comprehensive and robust dataset given the increase in the number of individuals
who volunteer to complete the SHARP survey.
Limitations of the Study
Despite the quality of data and close adherence to the data analysis plan, the study
had some limitations. Although the sample size for each survey year exceeded the
required number as determined by the G*power analysis (n = 568), the fluctuation in
overall survey responses warrants further discussion. One explanation for the fluctuation

might be the change in how the survey was administered. Starting in 2015, the SHARP
survey shifted from a traditional paper survey to an electronic survey conducted on
laptops and iPads (UDOH, 2018). This transition may have contributed to the changes in
the numbers of survey responses and explain the increase between 2015 and 2017.
A second limitation of this study was the potential bias created by a heightened
awareness of mental health among the parents and students after mental health
intervention efforts commenced. Sterne et al. (2016) noted that public health
intervention efforts could raise public awareness and increase reporting among the target
population. As a result, the increase in reported rates may overshadow the effectiveness
of public health efforts (Sterne et al., 2016). With students being empowered to identify
and discuss mental health due to the intervention efforts, the change in positive survey
responses may be the result of increased reporting and awareness, not necessarily the
ineffectiveness of local public health intervention efforts initiated by the CHA.
The concerns with increased reporting are exacerbated by the potential saturation
of responses from those with experience in mental health. Pursey, Burrows, Stanwell, and
Collins (2014) reported that studies evaluating the successes of postintervention efforts
are subject to response saturation by individuals in the target population who are
hypersensitive to the subject matter based on an eagerness to contribute. While the
increased participation is welcome, it does have the potential to skew research results
(Shaw et al., 2015; Short et al., 2009). As the discussion surrounding mental health
becomes socially acceptable, survey respondents interested in the mental health of

Summit County are more likely to participate in the survey than individuals with a lesser
interest. This is especially true given the voluntary nature of the SHARP survey. As a
result, this can lead to survey response saturation which could possibly misrepresent the
public health problem and the effectiveness of intervention efforts.
Finally, the many social factors that influence mental health were not accounted
for in this study. Gender, parental status, substance abuse, religion, and ethnicity have all
been shown to impact mental health (Viner et al., 2012). This premise of this study
focused on a presence-absence model using self-reported data without consideration for
extrinsic factors that impact mental health. While this research was the first step toward
addressing mental health in affluent communities, it was not a comprehensive overview
of the many variables that influence depression and suicide ideation in youth. However, it
does provide an avenue to enter the complex and dynamic field of mental health in the
affluent youth demographic.
Recommendations for Future Research
This emphasis of this study was the first to evaluate the effectiveness of
CHAdriven interventions on the youth of affluent communities by grade level and
geographic location. These findings help identify the need for additional research on
mental health in the youth of affluent communities. Future researchers should focus on
identifying what variables directly contribute to poor mental health outcomes in the
youth of affluent communities. An examination of all mental health challenges in the

youth of affluent communities by gender, parental status, substance abuse, religious
denomination, and ethnicity needs to be completed.
One such example could be the evaluation of challenges facing young men and
women to gain a better understanding of the potential influence of puberty and
maturation on the mental health of affluent youth. While this research was unable to find
significance in the variables selected, only a small subset of the variables known to
influence mental health outcomes were considered. There is still the potential to harness
the power of the SHARP dataset to evaluate the multitude of individual and social
variables that influence mental health in affluent communities.
There is a growing body of evidence indicating increased rates of suicide in
communities at higher elevations (Reno et al., 2017). Under the qualifying factors
provided by Reno et al. (2017), the elevation of Summit County would qualify as being
a risk factor for increased suicide ideation. While much of this research focuses on the
community as a whole, specific research into how elevation might impact suicide
ideation in the youth of affluent communities is warranted. Comparing rates of suicide
and suicide ideation in the youth of affluent communities at sea level to the youth of
affluent communities at elevations of 5000 feet above sea level may yield results that
identify environmental factors that contribute to the mental health of youth in affluent
communities. Building upon this growing body of evidence is a worthwhile effort that
will assist local public health agencies working with affluent communities.

Implications for Professional Practice and Social Change
This study has shown that the presence of depression and suicide ideation among
high school students in affluent communities cannot be teased out by grade or geographic
location. Additionally, it has shown that CHA-driven interventions can increase self-
reporting in affluent communities. While the limitation of response bias created by a
heightened awareness may have contributed to the inability to draw strong conclusions
about the effectiveness of the CHA-driven interventions, this research still benefits local
public health agencies by identifying ways the CHA process and DOI theory can be used
to raise awareness in affluent communities.
Implications for Public Health Practice
While the 19th century marked the great ‘sanitary awakening’ for public health,
the 21st century marks the expansion of public health into socially taboo fields like mental
health, suicide, depression, and opioid addiction. This transition from traditional public
health programs, like diabetes and tobacco cessation, to those that are socially taboo
creates a challenge for public health practitioners. The new wave of public health
challenges is non-selective and does not follow the social indicators, like socioeconomic
status, access to health care, and ethnicity, that are typically linked to reduced health
outcomes. Instead, all youth from all demographics are at risk for these new challenges,
which causes already thin public health resources to be spread even thinner. However,
public health will be challenged to find a solution at all federal, state, and local levels of
government.

The results of this research confirm that health agencies in affluent areas can no
longer assume that families with wealth and resources are not at risk for mental health
challenges. These findings provide evidence of mental health concerns in the youth of
affluent communities and further the need for local public health agencies to determine
the specific risk factors within their communities. This study determined that the
differences in self-reported depression and suicide between grades and geographic
locations were insignificant. However, this study also confirmed that there are youth
struggling with serious mental health problems every day. It should be expected that
mental health will continue to challenge public health. As a result, local public health
will continue to have a role in mental health using the results of studies like this one to
direct their efforts.
Implications for Positive Social Change
Positive social change occurs when the political and social wills merge with
science. This merger occurs as awareness lends way to public acceptance of the problem
at hand. From a public health standpoint, the result of this successful partnership is
disease control and eradication. However, this partnership must be amenable to all levels
and branches of the social structure. Although public health bears the majority of the
responsibility for education and awareness, there is also a social responsibility for
creating positive change. Local policymakers and community leaders must recognize the
problem at hand, become familiar with it, and accept the challenge that lies ahead.

However, this cannot be accomplished unless the right individuals are given the proper
instruments to guide the discussion.
For lasting social change to occur, it is imperative that research, much like this
study, be used to direct changes in how society views mental health. Messaging that
mental health can be managed much like physical health is key to social change. This
starts with data and evidence that place the interests of public health at the forefront of
the political discussion. Policymakers must be empowered to make decisions that benefit
their communities while remaining fiscally responsible. Without any one piece of the
equation, the likelihood of lasting, long-term change is unlikely. This study provides
local leaders with evidence of an existing problem and promotes the creation of policy
that drives permanent change while minimizing the stigma associated with mental
health.
While there is a definite political responsibility to allocate resources capable of
creating change, society must also be held accountable for evoking positive social change
around mental health. The presence of one child suffering from depression or suicide
ideation in any community exceeds the allowable social threshold. For families with
children struggling with mental health, any research into the problem brings the hope of a
brighter future. Additionally, it helps families understand that their youth are at risk,
despite the resources and wealth that might be available. These findings can help parents
take a keen interest in the mental health of their children. Additionally, the heightened
awareness created by the CHA intervention efforts can remove the stigma assigned to

mental health by creating opportunities for discussions about suicide and depression in
communities where they have been ignored. Although public health practitioners will
continue to work diligently to address mental health at the community level, the fulcrum
that balances mental health is based in the home.
Conclusion
Historically, public health agencies were developed to conduct and enforce
sanitation. Now, public health has evolved into a field that includes all aspects of
population health. Looking to the future, the constant evolution of public health is
demonstrated by the declaration that mental health is a significant public health concern
included under the public health umbrella. However, this addition should come as no
surprise given the success of public health programming. Reiss (2013) contends the
declaration of mental health as a public health epidemic is a turning point in the battle
against suicide and depression. With its variety of programs, public health continues to
experience success in managing infectious diseases and sanitation. When considering
mental health, similar outcomes should be expected.
Modern public health has been shaped by two factors: the growth of scientific
knowledge specific to controlling disease and the growth of public acceptance (Institute
of Medicine, 1988). The factors that contributed to this growth were accomplished by
providing sound evidence that gained social favor. As a result, public health has been
able to strategically approach disease control and prevention with time-tested and

refined processes. The structure provided by the theory-based approach has been key to
the success of public health.
To continue this trend of success in mental health, public health practitioners must
avoid disarray in program development. The success of the past must be used to direct
future public health efforts. By addressing gaps in data gathering, analysis, and
evidencedriven programs, the discipline of public health can align current efforts with
historical successes to improve mental health outcomes. It is the responsibility of public
health to provide the evidence that drives policymakers to action and community leaders
to campaign for change. To achieve this objective, public health will need to serve as a
catalyst for private efforts and initiate high-level health functions that only local
government can perform. Once these duties align, public health will assume its role as the
unquestionable leader in mental health.
The virtual elimination of many infectious diseases provides ample evidence of
the effectiveness of public health measures that join scientific knowledge with effective
social action. Improvements in mental health status must be the result of public health
activities based on vigorous, scientifically competent, politically astute, comprehensive,
and sustainable public health capacity. Good, effective public health happens when
science merges with political will. Studies, no matter the size or the results, provide
insight that encourages this union. Despite the political influence, public health is still a
social and science-driven field. Research must be the foundation that pushes public health
and mental health forward. While this study was unable to find significant variables that

contribute to poor mental health in the youth of affluent communities, it has helped to
determine and define the social significance of the problem. As a result, it can be used by
local public health agencies to help build a foundation that will continue the proud
tradition of success in public health practice as practitioners face the challenges presented
by mental health.

