


Association Between Mental Health problems,
Substance Use, and Social Support in Youth
Chapter 1: Introduction to the Study
Mental health problems are a major public health concern and may be associated
with substance use (Conway et al., 2018) and inadequate social support over time
(Holden, Dobson, Ware, Hockey, & Lee, 2015). Risk factors for mental health problems
are widely considered to include genetic-environmental and cognitive factors (Cheng et
al., 2014) and may be prevalent not only in the adult population but also among students
before they reach their adult years. Mental health problems among young adults, in
particular, may be associated with the level of social support available to the individual
and may also be associated with substance use (Cheng et al., 2014). Substance use in this
study referred to the use of legal or illegal substances without a prescription (Birkeland,
Weimand, Ruud, Hoie, & Vederhus, 2017). Manwell et al. (2015) define mental health
problems as the absence of mental disease, which includes the biological, psychological,
and social factors that could affect a person's mental state and their function in society.
Social support is a formal or informal relationship that an individual has with another
person (Joni & Leonard, 2013). Social support that comes from family members, friends,
and peers is considered informal social support, whereas when it comes from
organization and healthcare professionals, it is considered formal social support (Joni &
Leornard, 2013). Substance use and lack of social support can impact the young adult’s
sense of well-being and may result in mental health problems, which could create
substantial societal burdens.
Existing literature suggests that mental health is associated with substance use

(Amosu, Onifade, & Adamson, 2016; Conway et al., 2018) and social support (Milner,
Krnjacki, & LaMontagne, 2016) may vary across the overall population and affects all
age groups including the young (Milner et al., 2016). Substance use is a national
epidemic and a public health crisis that has increased in prevalence over time and places
the population affected at risk for early mortality and morbidity (Hopkins, Landen, &
Toe, 2018).
By examining the relationship between mental health problems, substance use,
and social support, for young adults before they enter their adult years, specific and more
focused interventions may be developed to promote mental health problems strategies
that may improve outcomes among the young population. If the correlates of mental
health are identified early in a young person’s life, interventions may be implemented
early, and thus help the youth with mental health problems to become more productive
members of the society (Costello, 2016) and thereby promote positive social change.
Chapter 1 of this dissertation includes the background of the study, problem statement,
purpose of the study, research questions and hypotheses, conceptual framework, nature of
the study, definitions, assumptions, scope and delimitations, limitations, the significance
of the study, significance to social change and the summary.
Background of the Study
Studies have been conducted examining the association between mental health
problems, substance use, and social support in the overall adult population (Amosu et al.,
2016; Firestone et al., 2015; Jibeen, 2016; Ni, Harrington, Wilkins-Turner, 2017; Zhuang
& Wong, 2017). These studies were conducted in schools, communities, healthcare
facilities, and prisons and are the basis for interventions currently used for the population

suffering from mental illness such as identifying youths who are vulnerable to ensure
prevention and put in place early interventions which increased health outcomes. Further
interventions and treatments addressing mental health problems are needed (Conway et
al., 2018) to ensure appropriate treatment and management of care.
Despite many studies on social support and substance use associated with mental
health in the overall population, there is a lack of research on social support, substance
use, and the relationship to mental illness or mental health problems among the young
(Cheng et al., 2014; Jibeen, 2016; Lakey, Vander Molen, Fles, & Andrews, 2016; Lerissa
et al., 2017; Levula, Wilson, & Harre, 2016; Mason, Zaharakis, & Benotsch, 2014).
Shahdadi,Mansouri, Nasiri, & Bandani, (2017) examined the association between
mental health and social support among university students and found an increase in the
number of university students experiencing mental health problems. Another study
conducted by Ni et al. (2017) showed that certain age groups, especially youths, were at a
higher risk for mental health problems following substance use such as drinking and
illicit drug use. Mason et al. (2014) and Shahdadi et al. maintained that there is a
relationship between social support, substance use, and mental health problems and that
this should be examined to identify potential risk factors. The authors found that
substance use among young adults has increased without a corresponding increase in
social support; therefore, it is necessary to conduct research on substance use, social
support, and mental health problems among youth. For this study, I examined the
relationship between mental health problems and substance use and social support by
using secondary data obtained from middle school (MS) and high school (HS) students
in the Maine Integrated Youth Health Survey (MIYHS; 2017).

Substance use is associated with social support. Individuals who have
compromised social support such as family and friends may experience the consequence
of substance use that may affect their well-being (Staton, Royse, & Leukfeld, 2007).
Because social support is considered a buffer for an individual who experiences life crises
(University of Minnesota, 2016), individuals who have adequate social support are less
likely to begin substance use in times of distress. This is because positive social support is
an enhancer of positive behavior that is needed to avert drug use.
Substance use is associated with mental health problems such as anxiety,
depression, and suicide (Amosu et al., 2016; Lerrisa et al., 2017; Mason et al., 2014).
Early use of the substance may lead to many health risks, which include mental health
problems (Henchoz et al., 2016). The use of substances could impact some physiological
pathways that manifest as untoward health consequences. For instance, the use of
nicotine-containing substances could lead to addiction, and addiction is known to be
associated with a mental health problem.
Problem Statement
Mental health problems are a major public health concern and may be associated
with substance use (Conway et al., 2018). Individuals who have inadequate social support
over time are at a greater risk of experiencing mental health problems compared to
individuals who have a strong social support system (Holden et al., 2015). Substance use
issues may intensify with inadequate social support (Milner et al., 2016). A limited
number of studies have examined the quality of social support among individuals with
mental health problems (Amosu et al., 2016; Henchoz et al., 2016; Wang, Davis,

Wootton, Mottershaw, & Haworth, 2017) and the co-occurrence between substance use
and mental health problems (Conway et al., 2018).
Demographic differences such as race may play a role in substance use and mental
health problems and may contribute to young adult access to health care services
(Conway et al., 2018). While the occurrence of mental health problems, substance use,
and social support are well studied in the adult population, little is known about the
degree to which social support impacts mental health problems and substance use or
abuse among teens in MS and HS age groups. Therefore, further research is needed to
examine whether mental health problems are associated with social support and substance
abuse in MS and HS aged children as well as whether the problem increases with age.
This study examined retrospective data from a state-wide survey of youth in
MS and HS for substance use and social support associated with mental health problems.
Purpose of the Study
Using secondary data from the MIYHS 2017, the purposes of my study were to
determine (a) the relationship between mental health problems and substance use among
youth who are MS or HS students, (b) the relationship between mental health problems
and social support in youth who are MS or HS students, and (c) the relationship between
substance use and social support in youth who are MS or HS students. Data from the MS
and HS MIYHS 2017 were obtained from the Maine Center for Disease Control and
Prevention (Maine CDC) for the study. The MIYHS collected the data using specific
surveys developed for their respective age groups (MIYHS, 2017). The results of this
current secondary analysis may help practitioners to develop focused age-specific

interventions for students at risk of mental health conditions secondary to drug use and to
plan prevention programs for school-aged youths.
Research Questions and Hypotheses
This dissertation addressed the following research questions:
•Research Question 1: Using the MIYHS dataset, what is the relationship between
mental health problems and substance use among youth who are MS or HS
students?
H01: There is no relationship between mental health problems and substance use
among youth who are MS or HS students.
Ha1: There is a relationship between mental health problems and substance use
among youth who are MS or HS students.
•Research Question 2: Using the MIYHS dataset, what is the relationship between
mental health problems and social support in youth who are MS or HS students?
H02: There is no relationship between mental health problems and social support
among youth who are MS or HS students.
Ha2: There is a relationship between mental health problems and social support
among MS or HS students.
•Research Question 3: What is the relationship between substance use and social
support in youth who are MS or HS students?
H03: There is no relationship between substance use and social support in youth
who are MS or HS students.
Ha3: There is a relationship between substance use and social support in youth
who are MS or HS students.

Theoretical Framework
Two theoretical frameworks were used in this study: Relation regulation theory
(RRT) and the self-medication theory. The RRT provides a conceptual framework that
helps in assessing the direct impact of social support on mental health outcomes (Lakey
& Orechek, 2011). This theory maintains that supportive interaction has a positive impact
on mental health outcomes (John & Louise, 2013). Most importantly, the RRT holds that
individuals improve their mental health through the diversity of relationships (John &
Louise, 2013). For instance, if youth defined communication, interaction, and relationship
as a way of gaining social support, their behaviors and beliefs about social support is that
supportive interaction has a positive impact on mental health (John &
Louise, 2013).
The second theoretical framework is the self-medication theory. This theory helps
to conceptualize the association between substance use and mental health problems
(Lerissa et al., 2017) and to better understand substance use associated with mental health
problems among youth (Khantzian, 2017). Self-medication theory was developed to
address the concern about substance use by looking at the psychological underpinning of
substance use (Khantzian, 2017). For instance, the self-medication theory identifies and
addresses psychobiological factors that may cause substance use problems (Khantzian,
2017). This theory helps in identifying the reasons individuals use substances and may
help address the associated between substance use and mental health problems
(Khantzian, 2017). More detail on the self-medication and RRT frameworks is presented
in Chapter 2.

Nature of the Study
This study was a cross-sectional, retrospective, correlational design using a
quantitative approach. For this study, I used data from the 2017 Maine Integrated Youth
MIYHS. In this study, the definitions used by the MIHYS were adopted and include
•mental health problem, measured as a sad feeling or suicidal ideation for the
past 2 weeks (MIYHS, 2017); and
•social support, measured by love and support from family as well as
communication with family and friends.
These are captured by the following two questions: (a) “I have a family that gives me
love and support” and (b) “I have parents who are good at talking with me about things”
(MIYHS, 2017). Substance use was measured using the following question: “During your
life, how many times have you used any form of cocaine, including powder, crack, or
freebase?” (MIYHS, 2017). The independent variables include social support, substance
use, and age group. The dependent variable is mental health problems. Other variables
that were included in the study are county and number of individuals in the household
and parent’s social, economic status. The age group categorized MS or HS years of age.
In my study, I used secondary data from the 2017 MIYHS to examine mental health
problems associated with substance use and social support among youths. The data were
analyzed through logistic regression in which mental health problems is categorized as
yes or no.
The study focused on the analysis of the MS and HS student data from the

MIYHS. The sampling frame includes all public and quasi-public schools in the state of
Maine that enrolled at least 10 students with kindergarten-third grade, fifth-sixth grade,
seventh-eight grade (MS), and ninth through 12th grade (HS).
Definitions
Mental health problems: Manwell et al. (2015) defined mental health problems as
the absence of mental disease, which includes the biological, psychological, and social
factors that could affect a person's mental state and their function in society. The World
Health Organization (WHO, 2014) defined mental health as an individual’s ability to
realize their potential to cope with normal life events and able to contribute to society.
Dependent variable for assessing mental health problems was sad feeling or suicidal
ideation for past two weeks (MIYHS, 2017). Participants who are reporting sad feelings
or suicidal ideation were coded as 1 and 0 otherwise.
Social support: A formal or informal relationship that an individual has with
another person (Joni & Leonard, 2013). Social support that comes from family members,
friends, and peers is considered informal social support, whereas when it comes from
organization and healthcare professionals, it is considered formal social support (Joni &
Leornard, 2013). It is when an individual has friends, family, peers, and others to reach
out to when in need to help the individual focus on a positive outlook (University of
Minnesota, 2016). Social support can enhance the quality of an individual’s life by
providing a buffer in times of crisis (University of Minnesota, 2016). The understanding
of social support is that the individual feels accepted, receives care, and assistance during
difficult times (Joni & Leonard, 2013). Free sharing of resources to help improve
wellbeing and to allow interaction between individuals is also a form of social support

(Joni & Leornard, 2013). Social support was measured by love and support from family
as well as communication with family and friends. Independent variables were: (a) I have
a family that gives me love and support, and (b) I have parents who are good at talking
with me about things (MIYHS, 2017). Participants who reported having a family that
gives them love and support or having parents who are good at talking with them about
things were coded as 1 and 0 otherwise.
Substance use: The use of legal or illegal substances without a prescription
(Birkeland et al., 2017). The independent variables of substance use were measured by
this question: “During your life, how many times have you used any form of cocaine,
including powder, crack, or freebase?” (MIYHS, 2017). Response participants who
reported using methamphetamines or ecstasy during their life was coded as 1 and 0
otherwise.
Secondary data: Data derived from primary data, which is used to answer
research questions that the data were not developed to answer (Shamblen & Dwivedi,
2010).
Middle school (MS): MS refers to youth who are in Grades 7 and 8.
High school (HS): HS refers to youth who are in Grades 9-12.
Assumptions
Assumptions provide a structure about the belief of the methodology,
understanding, and the reality of research (Russel, 1995). An assumption made in this
study is that the participants provided an honest and truthful response to the MIYHS
survey and that the data was collected correctly. The data source is reliable. An
assumption underlying one of the hypotheses is that a lack of social support among

individuals negatively impacts mental health, particularly suicidal ideation and depressive
symptoms. Individuals who keep to themselves are more susceptible to suicidal ideation
and depression than are individuals who interact with others within a positive social
circle.
Scope and Delimitations
The research study used a quantitative, cross-sectional, correlational design with
secondary data from the MIYHS to examine mental health problems associated with
substance use and social support among youth. The MIYHS was conducted by the Maine
Department of Education who collaborated with the Maine CDC and Substance Abuse
and Mental Health Services in the Department of Health and Human Services (MIYHS,
2017). However, the survey is administered by the Pan Atlantic SMS Group administered
to youths who are in school. The survey was conducted in 2015 to assess the risk
behaviors of the Maine’s youth (MIYHS, 2017).
Secondary data are collected by someone else, such as a government agency,
schools, or recordkeeping organizations (Steve, 2017). The use of secondary data is less
time consuming and more cost-effective (Steve, 2017). Secondary data can be easily
accessed through existing data sources (Steve, 2017). Even though the study uses the
public and quasi-public schools in the state of Maine that enrolled at least 10 students,
there are some limitations because students who are homeschooled would not be
captured. The demographics of youth in Maine might not represent the demographics of
all youth in the United States. Therefore, the result might not be generalizable to the
United States population. This study focused on middle and high school students because
this is the age at which they are transitioning to young adults. The association of mental

health problems with substance use and social support were only considered at the public
school of Maine. Some of the population of the public school of Maine was excluded due
to grades. The excluded grades were grades below kindergarten-third grade. The
theoretical framework for understanding the association between mental health, social
support and substance use in excluded population is the social ecological model of human
development. This model is conceived as a set of nested structure for understanding
factors (social, emotional, etc.) that influence individuals’ development at varying degree
(Trach, Lee, & Hymel, 2018).
Limitations
This study was a descriptive, correlational study that assessed association between
mental health and substance use and social support in youths. The identification of
association does not mean there is causation between the variables (Seema, 2018). This is
a limitation because there might be other possible explanations for any observed
association. For example, an unknown genetic factor may be associated with mental
health, and the same genetic factor may associate with substance use (Adibsereshki,
Abdollahzadeh, Hassanzadeh, & Tahan, 2018). Therefore, the observed association might
be due to an unknown confounding factor. To address the limitation of confounding
factors, for this study, I controlled for covariates that may be associated with the key
variables of social support, substance abuse, and mental health problems. I controlled for
number of adults over 21 known to participants who in the past year have used marijuana,
crack, cocaine, or other drugs. The study results are from only Maine and may not be
generalizable to young adults in the whole United States. Some schools in Maine were
not able to participate in the survey due to grade reconfiguration or closing of the school

(Maine CDC, 2017). Therefore, the modules for the Grades K-3 and 5-6 were replaced by
an eligible school that may only closely match the schools that were ineligible for the
study. Therefore, an adequate and representative sample may not be available for the
study. Schools that failed to respond to the survey were also replaced by another school
that was chosen randomly to replace those nonresponding schools.
The MIYHS has a limitation because the study only focused on youth in school
(Maine CDC, 2017). Therefore, youths who are dropouts, absent, home-schoolers,
homeless, and runaway youth were missed or no response (Maine CDC, 2017). Some
schools had a small number of students who were enrolled in Maine’s island or rural
areas which led to non-response to survey due to exclusion (Maine CDC, 2017). The
language barrier is a limitation because the questionnaire is anonymous and was not
administered in multiple languages (Maine CDC, 2017). Therefore, individuals with
limited English language may not respond to the survey (Maine CDC, 2017). Another
limitation barrier is that teachers are not allowed to help students fill out the survey
stemming from confidentiality and to maintain consistency in the way the questions were
developed (Maine CDC, 2017). Therefore, students who are experiencing disability in
reading and cognitive impairment may not complete the survey or response to the survey
(Maine CDC, 2017). There may be bias due to self-reporting because the participants
may forget, deceive, or may not understand the questions, which may lead to
underreporting or overreporting (Maine CDC, 2017). Nonetheless, studies have shown
that surveys completed by young adults could provide valid and reliable information that
is needed for research (Maine CDC, 2017).

Significance of the Study
Identification of whether or not social support and substance use are associated
with mental health problems will help policymakers to develop better mental health
policies. The result of this analysis could help practitioners develop focused age-specific
interventions for students at risk of mental health conditions secondary to drug use and to
plan prevention programs for school-aged youth.
The self-medication theory may be used to identify strategies that will help
address the psychobiological factors that contribute to substance use problems (Tronnier,
2015). This study may generate data to better understand the nature of the
interrelationship between substance use, social support, and mental health problems (Hall
& Queener, 2007; Tronnier, 2015) and may help the practitioner develop an intervention
for youths experiencing substance use problems. The RRT may be used to understand an
individual’s social support perception about social support and its benefits to better health
outcomes (Woods Lakey, & Sain, 2016). By understanding social support and its
benefits, practitioners may develop ways to improve social support that will help buffer
stressful events; individuals may experience in their lives (Cohen & Will, 1985).
Therefore, the RRT may extend to practice to help youth access the social support needed
for their well-being. Evidence-based practice may help improve individual health
outcomes, so the study on mental health problems association with substance use and
social support may identify and buttress the need for intervention that can be used to
bring about positive social change in society. This may help an individual from
experiencing worsening of mental health problems that may lead to unproductive life in
society (Castello, 2016). In all, this study may contribute to the existing body of

knowledge on how the prevention of substance use and the promotion of social support
could lead to an improvement in mental health outcomes.
Significance to Theory
Khantzian et al. (2017) provided information on the self-medication theory that is
used for the psychological underpinnings of substance use that may lead to mental health
problems.
The concept of self-medication is used to identify ways to address
psychobiological factors that may cause substance use problems (Tronnier, 2015).
According to Tronnier (2015), self-medication theory provides a broader understanding
of substance use by individuals. Self-medication theory was used to explained substance
use association with mental health among youth (Hall & Queener, 2007). Woods et al.
(2016) used the RRT to predict the main effect of perceived support based on activity that
is shared. The RRT is used to understand better how social support is necessary to
prevent a mental health problem. The study examined mental health problems association
with substance use and social support among youth from the public and quasi-public
schools in the state of Maine but can be used in many facilities, also applying the
selfmedication theory and RRT in clinical practice.
The conceptual framework was used to strengthen the understanding of the
relationship between mental health problems, social support, and substance use in youth.
The theory used in this current study might not apply to other populations, such as young
adults or older adults, because the theory in this study was based on the youth population
only.

Significance to Practice
Public health professionals are in constant need of evolving empirical evidence to
inform evidence-based practice guidelines that will help improve patients’ health
outcomes. If an association between mental health and (a) social support and (b)
substance use among youth is identified, early intervention can be developed to improve
positive health outcomes. If an association is found to exist between mental health
problems and social support, it will provide data to show the importance of ensuring that
individuals with mental health problems have access to the social support that they need.
Moreover, any association found in this study will call attention to the merit of continued
sharing of data with practitioners who are in the best position to implement an
intervention that is needed to improve mental health outcomes.
Significance to Social Change
By evaluating the association between mental health problems, substance use, and
social support, specific and more focused intervention can be developed to promote
mental health outcomes. If these correlates of mental health problems are identified early
in young adults’ life, an intervention can be implemented early, and this will help youth
with mental health symptoms become more productive in society (Costello, 2016). If the
youth with mental health problems receive needed intervention early, this may help
worsening of the mental health problem, which could have an untoward effect on the
family, community, and population at large. Early intervention will not only help the
youth live a more productive life, but it will also help avert future negative effects of
mental health problems, including but not limited to the cost of hospitalization and the
youth inflicting harm on themselves. This will, without a doubt, bring about positive

social change in society (Costello, 2016). Early intervention in preventing substance use
among youth that may lead to mental health problems will increase positive social change
for the individual, community, and in the population (Spoth, Trudean, Redmond, & Shin,
2014).
Summary and Transition
Mental health problems continue to be a problem in society, and youth in the
public school in Maine experience the same problems (Milner et al., 2016). This study
focused on mental health problems associated with substance use and social support
among youths. There may be an increase in the number of youths experiencing mental
health problems associated with substance use and inadequate social support among
youths (Spoth et al., 2014). Even though there are many studies in other populations,
there is limited understanding when it comes to mental health problems associated with
substance use and social support among youths in public schools in Maine (Milner et al.,
2016).
Chapter 2 will present the review of the literature on mental health problems
association with substance use and social support.
Chapter 2: Literature Review
Using secondary data from the MIYHS 2017, the purpose of my study was to
determine (a) the relationship between mental health problems and substance use among
youth who are MS or HS students, (b) the relationship between mental health problems
and social support in youth who are MS or HS students, and (c) the relationship between
substance use and social support in youth who are MS or HS students. Existing literature
suggested that mental health problems are associated with substance use (Amosu et al.,

2016; Conway et al., 2018) and social support (Milner et al., 2016) in the adult or overall
population. However, the association between mental health problems and social support,
as well as between mental health problems and substance use varied between the overall
population and young adults (Milner et al., 2016).
Despite many studies on the association of social support and substance use with
mental health in the overall population, no research was identified showing that the
variables were associated among MS- and HS-aged children (Cheng et al., 2014; Jibeen,
2016; Lakey et al., 2016; Lerissa et al., 2017; Levula et al., 2016; Mason et al., 2014).
Therefore, the gap in knowledge regarding the association of social support and substance
use with mental health problems among young adults, including middle and high school-
aged children, was the focus of this current study.
In this literature review, I evaluated previous studies regarding mental health
problems and their association with substance use and social support. This chapter
presents the literature search strategy, literature review on mental health problems, social
support and substance use, theoretical framework, summary, and conclusion.
Literature Search Strategy
The databases used for the literature review include CINAHL Plus with full text,
Medline with full text, Proquest dissertations and theses, Proquest Nursing and Allied
health sources, Pubmed, CINAHL and Medline combined sources, Ovid full-text nursing
journals, and Psychology full-text sources. The key terms and phrases used for the
literature review included mental health problems, mental health, social support,
substance use, substance abuse, substance use/abuse intervention, MIYHS, suicidal
ideation in youths, sad feelings, and social support interventions.

The articles used for the literature review search included peer-reviewed articles
that describe mental health problems and their association with social support and
substance use in public and quasi-public schools and published from 2000 through 2018.
Much of the literature on the association of mental health problems with substance
use and social support focused on adults, college students, and prisoners, whereas a small
number of articles focused on mental health problems that may be associated with
substance use and social support in public schools (Amosu et al., 2016;
Cheng et al., 2014; Holden et al., 2015; Lerissa et al., 2017).
Theoretical Framework
Two theoretical frameworks were used to guide the study: the theory of
selfmedication and the RRT.
Theory of Self-Medication
Khantzian’s (2017) and David’s (1974a) theory of self-medication was used to
guide substance use treatment, so I used it in examining substance use in the current
study. Khantzian and David developed the theory to assess and treat drug addiction
problems. The self-medication was in the context of regulation where an individual’s
sense or understanding of regulation matches self-medication. When self-medication is
applied to substance use in public and quasi-public schools, the theory may be better
understood.
The self-medication theory proposed that there is an underlying reason for drug
use. Although Khantzian and Duncan are credited as the originators of the selfmedication
theory, Fenichel (1945) and Rado (1957) suggested that pressure was an underlying
motivation for drug use. Other authors, such as Glover (1956) and Ronsenfeld (1965),

have also contributed to this theory. The Khantzian model of self-medication presupposes
that drug addiction results from inadequate ability to control aggression; therefore, the
drug addict resorts to a drug as a way of controlling their aggressive drive, which leads to
physical dependency (Khantzian, 1997b, 1999). This self-medication hypothesis, which
originally included cocaine, was subsequently expanded to alcoholism and later
developed into a theory (Khantzian, 1997a, 1999). The fully developed selfmedication
hypothesis asserts that drug addiction results from venerable self-medication (Achalu,
2002).
Duncan’s (1974a) version of self-medication, rooted in behavioral theory, makes a
distinction between drug use and drug abuse. Duncan asserted that many of the illegal
drug users do not qualify as a substance abuser and that the majority of drug users have
control over their drug use. Duncan’s model is concerned with drug use without a
prescription, which could expose the individual to health risk. Duncan maintained that
drug use results from the pleasurable effect of the drug. Duncan’s model attempted to
explain drug dependence, a term used to replace the term addiction. The theory will help
explain the reason youths are using a drug that can lead to mental health problems, which
is a health risk.
Theory of Relational Regulation
Lazarus and Folkman’s (1984) RRT is used to explain how social support helps
individuals manage stress that they may be experiencing in their lives. However, enough
support is needed to help the individual cope with the stressor. The stress and coping
version of the RRT can explain stress-buffering effects but not the main effect of stress.
Therefore, the main effects of perceived social support associated with mental health

problems are likely to increase and multiply at a steadier pace than do the buffering
effects, so the stress and coping theory are not able to appropriately explain the main
effects of perceived social support associated with mental health problems (Lazarus &
Folkman, 1984).
The RRT maintained that individuals who think they have someone to assist them
in their times of need have better mental health outcomes than those who perceived low
social support. The purpose of RRT was to explain the main effect of perceived support
on mental health because this effect could not be explained by stress and coping theory.
The rationale in the use of RRT is that the association between social support and mental
health originates from people regulating their emotions through shared activity and
conversation. RRT has been found to have both buffering and a direct effect on mental
health. The regulation of emotion is relational because personal taste determines the topic
of conversion, activities, and providers of support (Lazarus & Folkman, 1984).
Cohen and Wills (1985) differentiated between stress-buffering and the main
effect, which is the foundation of the RRT. Stress buffering happens when an individual
has someone to protect them from the stress they are experiencing. Therefore, the main
effects happen when individuals have high social support with better mental health
outcomes, while other individuals have low social support, even with or without stress.
The stress-buffering theory, a version of the RRT, was developed to explain the social
support associated with mental health, which reflects stress buffering. Many authors,
including Barrera (1986), Cohen and Wills, Cutrona and Russell (1990), and Thoits
(1986), contributed to the development of the stress-buffering theory.
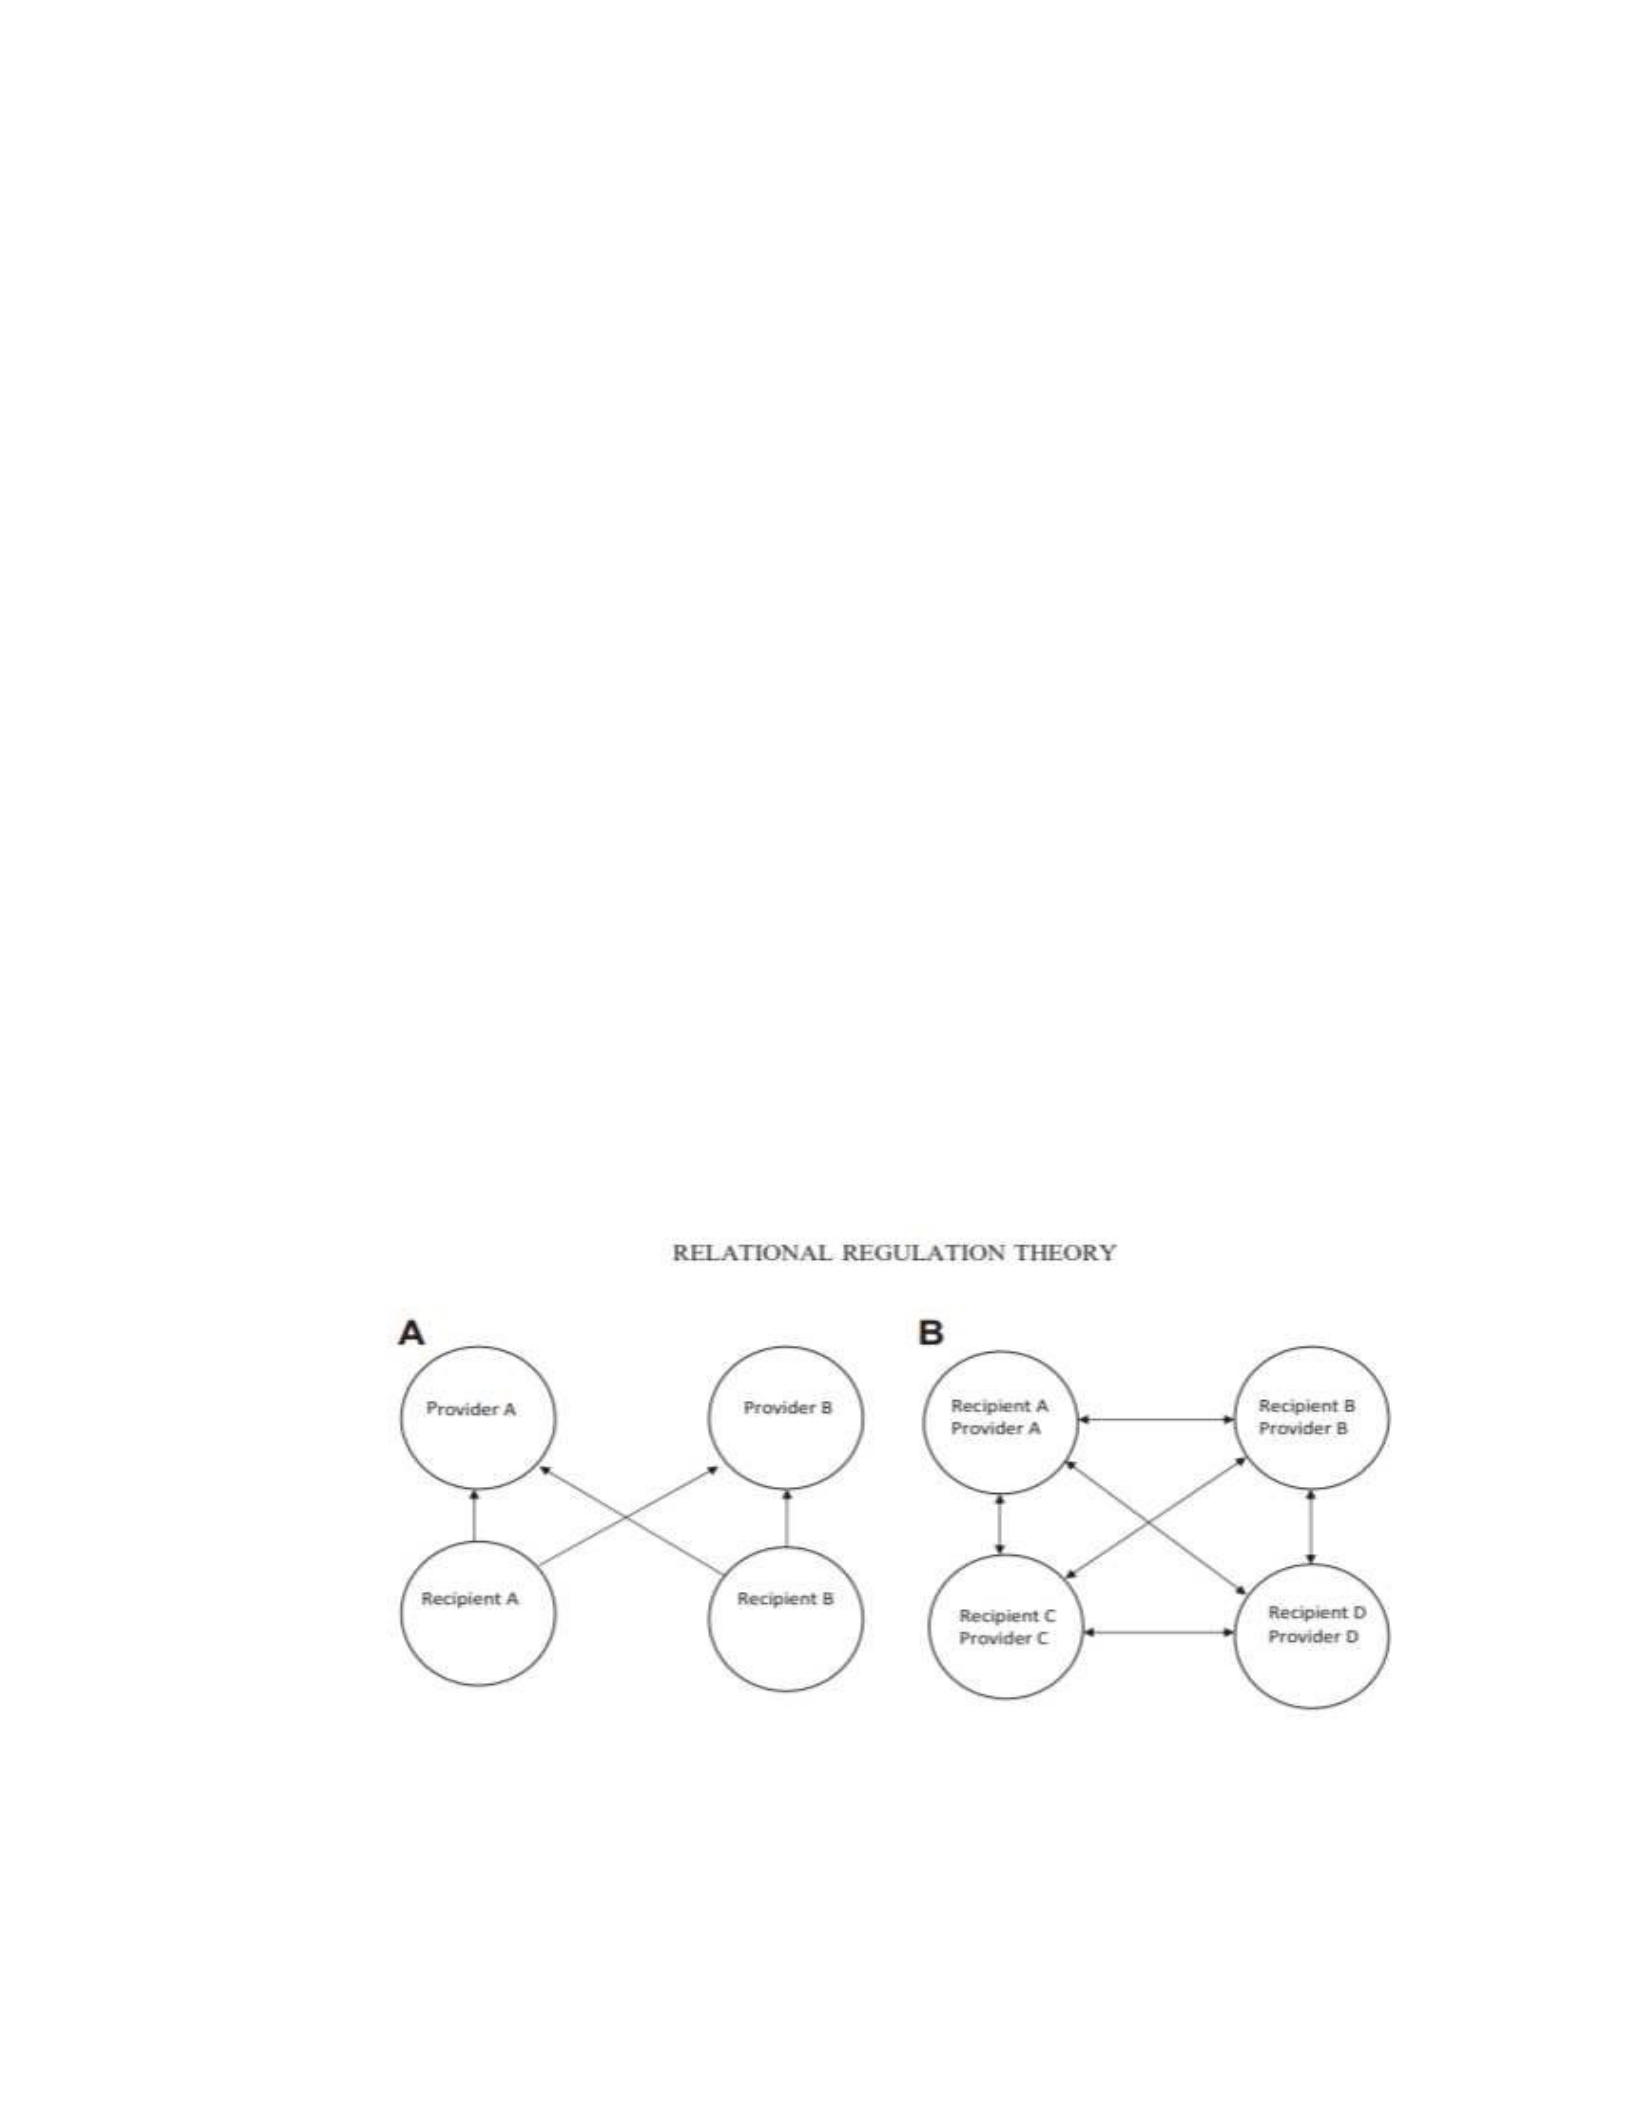
This stress-buffering theory is an extended version of the stress and coping theory,
developed by Lazarus (1996) and Lazarus and Folkman (1984). The stressbuffering
theory may be summarized into five different factors, such as life events, increased events
risk, the stability of social support, availability of social support, and how effective the
social support was able to relieve the stress. Even though the stressbuffering theory has
been used in many areas of research, there are empirical limitations because this theory
only evaluates inconsistency. However, Brown and Harris (1978) found consistency in
the stress-buffering theory. Figure 1 illustrates the RRT; the rationale in the use of RRT is
that the association between social support and mental health originates from people
regulating their emotions through shared activity and conversation. RRT has been found
to have both buffering and a direct effect on mental health. The regulation of emotion is
relational because personal taste determines the topic of conversion, activities, and
providers of support (Lazarus & Folkman, 1984).
Figure 1. Schematic representation of the relational regulation theory (RRT). Designed
for social support research.

Literature Review Related to Key Variables and Concepts
The literature review results are organized by the key variables and concepts:
mental health; social support; substance use; MIYHS; the association between mental
health and substance abuse; the association between mental health and social support; the
association between substance use and social support; existing approaches in the study of
mental health, substance use, and social support; theoretical framework; limitation of
previous approaches; the rationale for variables in this study; and the gap.
Mental Health
Mental health problems are a significant public health concern and are considered
to be a huge disease burden among young people in society (Cheng et al., 2014; Manwell
et al., 2015). As noted by Cheng et al. (2014), mental health is an individual’s state of
well-being, where these individuals understand their potential, can cope with daily stress
in their daily life, be productive, and contribute to their community. Mental health
problems in adolescents are considered to be strongly related to mental health in
adulthood.
These health problems can be influenced by biological and psychosocial factors
(Cheng et al., 2014; WHO, 2014). Other risk factors that affect mental health include
genetic, cognitive, temperamental, interpersonal, and family environment (Cheng et al.,
2014). In young adults, mental health problems impact educational achievement,
substance use, violence tendency, reproduction, and sexual health (Cheng et al., 2014).
Therefore, it is necessary to study the risk and the protective factors for mental health
problems among adolescents; such a study will help develop effective prevention
strategies (Cheng et al., 2014; Conway et al., 2018).

Social Support
Social support is an essential factor that helps the individual cope with changes in
their lives (Wang et al., 2017). Social support may help to alleviate distress and provide
hope in a time of distress (Cheng et al., 2014). Lack of social support can negatively
impact children and young adults’ life, especially those exposed to stressful life events
(Cheng et al., 2014). Providing social support in the family and the community may help
decrease distress and promote hope. Social support is crucial in early adulthood (Holden
et al., 2015). Individuals who lose their social networks are at risk for illness (Levula &
Harre, 2016).
Social support differs not only by gender but also by age. Women are more likely
than men to give and receive social support, to have more social friends, and to focus on a
social network (Milner et al., 2016). Relying on social group changes as individuals get
older. For example, adolescents have more social networks than older people (Milner et
al., 2016).
Substance Use
Substance use is a problem worldwide, and it is a risk factor for many health
problems. For example, cannabis is used illegally worldwide at a rate of 3.9% among
individuals aged 15-64, and it increases school dropout and motor vehicle accidents
(Henchoz et al., 2016).
Research shows that young adulthood is a crucial stage for substance use (Mason
et al., 2014), and young adults are more likely to drink heavier than older adults (Mason
et al., 2014).

The negative impact of substance use includes an increase in the cost of
healthcare, crime, and the yearly loss of productivity (Lerissa et al., 2017). Not only are
the financial costs a problem, but more importantly, substance use may predict health risk
behaviors that can cause long term negative health outcomes that include decreased
mental health (Amosu et al., 2016). Individuals who use substance sometimes face
memory problems, clear thinking and decreased attentiveness (Lerissa et al., 2017) which
affects youths, particularly at a vulnerable time because of neurodevelopment. Substance
use may affect the process peak and the function of neural development that alters the
youth's academic and social functioning (Henchoz et al., 2016).
Preventative measures are necessary to decrease health risks and prevent the
progression of multiple substance use (Henchoz et al., 2016). There is a need to
implement programs and policies that discourage early substance use.
Maine Integrated Youth Health Survey
The MIYHS was developed in 2009 to make an improvement in data quality,
decrease the financial burden for Maine schools and expenses (MIYHS, 2017). MIYHS
allows multiple survey requests while providing many health topics about youth
(MIYHS, 2017). The survey was administered in February 2015 (MIYHS, 2017).
The MIYHS was created and implemented in 2015 through collaboration between
the Maine Department of Education and the Maine department of health and human
services (MIYHS, 2017). The Pan Atlantic Research of Portland, Maine distributes the
2015 Youth Health Survey (MIYHS, 2017). Four surveys were composed and given to
students according to grades (MIYHS, 2017). The middle school and high school survey
collected data on many topics including mental health, social support and substance use

(MIYHS, 2017). The school must meet specific criteria in order to be eligible to
participate in the survey (MIYHS, 2017).
Association Between Mental Health Problems and Substance Use
Mental health and substance use are problematic because they are associated with
poor health outcomes, and about 20% of children and adolescents experience mental
health problems such as depression because of substance use (Cheng et al., 2014; Lerissa
et al., 2017). The use of a substance can adversely affect an individual’s mental health;
these health consequences from substance use extend to the increase of anxiety (Amosu
et al., 2016). An individual that is experiencing mental health problems along with
substance use is considered to be a co-occurring disorder. Depression is a major
contribution to substance use in individuals. Many individuals use substance use as a way
to cope with mental health (Lerrisa et al., 2017). Excessive substance use, such as
alcohol, may be associated with a mental health problem such as suicide, and young
adults with depression have a higher risk of comorbidity with suicidal ideation, anxiety,
and substance use (Mason et al., 2014).
Almost 20% of individuals with a mental health problem develop a substance use
problem in their lifetime, and about 55% of the individuals with mental health and
substance use get no treatment, while about 7.4% with both disorders received treatment
(Lerrisa et al., 2017). Some barriers prevent help-seeking for mental health and substance
use problems such as the stigma of mental health problems, lack of understanding about
mental illness in parents and young people, cultural competency, the financial cost, while
many individuals with mental health, alcohol, and substance use problems do not seek
help (McCann, Mugavin, Renzaho, & Lubman, 2016).

Association Between Mental Health Problems and Social Support
Worldwide, individuals are at higher risk for mental health problems that may be
associated with social support (Cheng et al., 2014). Social support contributed to the
mental health of individuals. Social support throughout young adult life may contribute to
psychosocial wellbeing in individual adult life (Holden et al., 2015). Social support
decreased the mortality rate and increased better mental health outcomes in individuals,
and early social support may help prevent mental health in adulthood (Holden et al.,
2015). Positive social support associated with mental health varies with gender financial
status and an individual stage in their life. However, people with poor social support may
experience poor mental outcomes and well-being (Holden et al., 2015). Social support
and mental health vary with gender, socioeconomic status, and the stage of life (Holden et
al., 2015). Poor social support and mental health may affect individual well-being as the
individual ages, and a decrease in social support affect one's mental health, while high
social support provides better mental health outcomes (Holden et al., 2015; Shahdad et
al., 2017). Social support can minimize daily stressor, and this can protect and improved
mental health outcomes (Shahdad et al., 2017).
Association Between Substance Use and Social Support
Substance use and social support affect an individual’s well-being. Social support
helps decrease the rate of substance use (Holden et al., 2015; Studer et al., 2017). Poor
social support from spouse, family, and friends put an individual at risk for substance use.
However, the benefits of social support depend on the type of support the individual
received (Studer et al., 2017). College students with no positive social networks are at
high risk for using substance, including alcohol, tobacco, and marijuana, while support

from friends who use substances may increase an individual’s risk, support from spouse
and family may be protective to prevent substance use ((Mason et al., 2014; Studer et al.,
2017).
Existing Approaches in Study of Mental health, Substance Use, and Social Support
Research Approach
Milner et al. (2016) assessed the association between social support and mental
health by age and gender using 13 years of cohort data. The authors used mental health
Inventory-5 (MHI-5). A social support scale was used which composed of 10 items. A
change in mental health was assessed using longitudinal fixed effects regression model
controlling for time. Results suggest that a higher level of social support helps improve
mental health. A cohort study using risk factors (C-SURF) and longitudinal study design
to assess risk and protective factors for substance use in adulthood (Studer et al., 2017).
The perception of social support was examined using a multidimensional scale (Jibeen,
2016). The MSPSS that consist of 12-items that got a score on a 7 point li kart-type scale
ranging from 1 through 7, where one strongly agrees, and seven is strongly disagreed
(Jibeen, 2016). Results showed that the coefficient of correlation that mental health
problems increased with the low level of familiar social support (Jibeen, 2016). The
authors assessed the differences in mental health and substance use among gender and
education levels using 634 American Indians from the Eastern Tribe (Ni et al., 2017). The
study analysis used logistic regression analysis of variance. The study showed that men
self-rated better mental health but binge drank and used illicit drugs more frequently than
females. Individuals who had a post-high school degree had better mental health than
individuals who did not have a high school diploma. The increase in education decreased

the use of a substance such as cigarette smoking. Illicit drugs include marijuana, cocaine,
and LSD.
Theoretical Framework
The theories used for this study is the strengthening families program for youth
10-14 and life skills training, and the life skill training is based on social learning theory
(Spoth et al., 2014). Personal social network framework used to understand better
substance use intervention and their supportive and unsupportive network to assess
participant’s behavior and their recovery (Tracy, Munson, Peterson, & Floersch, 2010).
The study used the risk, and the protective factors for mental health problems and the
impact on cultural and geographical variations have on mental health outcomes on
adolescents to help develop effective prevention strategies, and psychosocial factors help
determine an individual’s well-being (Cheng et al., 2014; Levula et al., 2016). The study
assessed the association between mental health scores and social network factors on
mental health across different life stages (Levula et al., 2016).
Rationale for Variables in this Study
The youth health survey (MIYHS) was used to improve data quality, decrease
collection expenses, and decrease survey burden on Main schools (MIYHS, 2017). The
collaborative survey decreased the burden on schools by using several survey requests
and gives local and state-level data a broad range of health topics about youths (MIYHS,
2017).
The tool that was used to collect the self-reported data can use in schools to assess
risk behaviors and protective factors of youths in society among states and nationwide
level data (MIYHS, 2017). The variables can be used by districts to create policy change

in school, shows a connection between youth academic performance, health risk
behaviors, schools climate problems, and help in getting grants for school programs
(MIYHS, 2017). Longitudinal studies found that social support may predict the outcome
of mental health problems (Holden et al., 2015). Low friendship security is related to
poor mental health outcomes, which include depressive symptoms (Mason et al., 2014).
Gap
More research is needed to address mental health problems in young people living
in already challenge with competing health and social burden and should not be neglected
(Cheng et al., 2014). More research is needed for substance use and mental health for the
implementation of early intervention for better health outcomes for youths (Conway et
al., 2018). My study is needed to examine the social support network properties across
different stages of life and not just in isolation of one another, and the influence of peer
networks on mental health symptoms among college students has been less studied.
Therefore, further research on the development of interventions that target the social
context of health is needed (Levula & Harre, 2016; Mason et al., 2014).
Summary and Conclusions
Mental health problem has been shown to be associated with substance use and
with a lack of social support, but little research has examined the problem among the
youth. Therefore, there is a gap in the examination of social support and substance use
and their association with mental health problems among youths. The databases used to
find full-text sources on mental health, substance use and social support include:
CINAHL Plus with full text, Medline with full text, Proquest dissertations and theses,

Proquest Nursing and Allied health sources, Pubmed, CINAHL and Medline combined
sources, Ovid full-text nursing journals, and Psychology. I used secondary data and
quantitative methods to examine the association between substance use and social
support. Two conceptual frameworks, the self-medication theory and the RRT served as a
foundation for understanding mental health problems and their association with social
support and substance use.
Chapter 3 presents the research design and rationale, methodology, including
population, sampling procedures, archival data, instrument, reliability, and validity. The
analysis tool and the data analysis used to analyze the data are explained.
Chapter 3: Research Method
Using secondary data from the MIYHS 2017, the purpose of my study was to
determine (a) the relationship between mental health problems and substance use among
youth who are MS or HS students, (b) the relationship between mental health problems
and social support in youth who are MS or HS students, and (c) the relationship between
substance use and social support in youth who are MS or HS students.
Chapter 3 will present the research design and rationale. The methodology
includes population, sampling procedures, and archival data, as well as the chosen
instrument, reliability, and validity. The analysis tool and the techniques used to analyze
the data are explained.
Research Design and Rationale
The study was a cross-sectional, retrospective, correlational design. For
assessment of the association between mental health problems with social support or with
substance use, the independent variables are social support and substance use, whereas

the dependent variable is a composite of mental health problems (suicidal ideation or sad
feelings). For the assessment of the association between substance use and social support,
the independent variable is social support, and the dependent variable is substance use.
There was no time constraint except the time necessary to get the secondary data
from the Maine CDC. The results of this quantitative, correlational study may help
provide a better understanding of the relationship among mental health problems, social
support, and substance use, and the type and strength of the relationship. Hence, results
from this study may provide strategies that support youth in the community by reducing
the risk of mental illness and substance-abuse-related outcomes while promoting social
support for youth. The MIYHS (2017) data can be used to identify the strengths and
challenges facing young people in society.
Methodology
This study involved a secondary, quantitative correlational analysis of data from
the MIYHS to determine the association of variables related to mental health problems,
substance abuse and social support. The sampling frames for the MIYHS comprised
Maine’s public and quasi-public schools that enrolled at least 10 students. The
questionnaire was administered to all students in the school districts in the state. Students
were required to answer the questions after consent forms were signed by parents. To be
eligible to participate in the MIYHS study, the students had to be in kindergarten-third
grade, fifth-sixth grade, seventh-eighth grade (MS), and ninth through 12th grade (HS).
The MS and HS surveys included four versions each (i.e., Version A, Version B, Version
C, and Version D).

Population
The population used for this study was drawn from the MS and HS students’
responses to the questionnaire in the state of Maine .Although other grades were included
in the original study survey, they were not included in the current secondary data
analysis. Access to the MIYHS data set required the principal investigator’s signed
confidentiality agreement, the institutional review board (IRB) approval, and project data
supervisor approval. I contacted the organization and spoke with the representative who
granted access to the data.
Sampling Procedures
A stratified random sampling was used to conduct the original study and included
all Maine’s public schools, quasi-public schools, and private schools that received about
60% of public funds (MIYHS, 2017). Schools with fewer than 10 students were excluded,
as were schools with alternative education and youth development centers. Schools that
did not respond were replaced by schools that were randomly selected from the sample
interval (MIYHS, 2017).
Archival Data
To gain access to the MIYHS data set, I signed a confidentiality agreement from
the CDC. I also secured IRB approval before commencing the study. Because this study
uses secondary data analysis, no informed consent was needed for the current study.
However, authorization was needed from the Maine CDC to use the data set.
Instrumentation and Operationalization of Constructs
For this study, I used secondary data analysis with no direct interaction with
participants. The data were collected by the Maine CDC using the MIYHS, which was

developed and implemented in 2015 by the collaborative effort of the Maine Department
of Education and the Maine Department of Health and Human Services. Four different
questionnaires labeled Versions A, B, C, and D were used to obtain information from
participants. Many questions used in the MIYHS survey were taken from other national
surveys. Some of the questions were taken from the National Youth Risk Behavior
Survey (YRBS). The reliability and validity of the YRBS questionnaire were conducted
by the Centers for Disease Control and Prevention (CDC, 2004) using two test-retest
reliability studies. One study was done in 1992, and the second study was done in 2000
(CDC, 2004).
Kappa was equal to 61%-100%, with no statistically significant differences
between the prevalence estimates for the first and second times the questionnaire was
administered. Kappa is used to measure the validity and reliability of the instrument
(CDC, 2004). Ten items (14%) had both Kappa less than 61% and significantly different
time-1 and time-2 prevalence estimates, which indicates that the reliability of those
questionnaire items is questionable (CDC, 2004). The CDC asserts that the validity of
adult self-reporting of behaviors measured by YRBS is not threatened by cognitive and
situational factors (CDC, 2004). Responses from the 7th_grade students were less
consistent than those from students in higher grades, suggesting that the questionnaire is
best suited for students in Grade 8 or higher (CDC, 2004).
The MIYHS survey results were appropriate for my study because the variables
used in my study were available from the question asked in the MIYHS and the variables
provided the answers to the questions that were used in the study to assess the association

between mental health with social support and substance use. The construct assessing
mental health, social support, and substance were taken from the MIYHS questionnaire:
Mental Health
•Item 14: (Have you ever seriously thought about killing yourself).
•Item 18: (During the past 12 months, did you ever feel so sad or hopeless
almost every day for two weeks or more in a row that you stopped doing
some usual activities);
•Item 20: (During the past 12 months, did you ever seriously consider
attempting suicide).
Substance Abuse
•Item 32: (Have you ever used an electronic vapor product), and
•Item 45: (About how many adults over 21 have you known personally
who in the past year have used marijuana, crack, cocaine, or other drugs).
•Item 63: (During the past 30 days, how many times did you take a
prescription drug (such as Oxycodone, Percocet, Vicodin, Codeine,
Adderall, Ritalin, or Xanax) without a doctor’s prescription).
•Item 69: (During your life, how many times have you used any form of
cocaine, including powder, crack or freebase), and
•Item 85 (About how many adults over 21 have you known personally
who in the past year have used marijuana, crack, cocaine, or other drugs).
Social Support
•Item 107: (I have support from adults other than my parents),

•Item 108: (I have a family that gives me love and support) are included in
the construct for social support.
(See Appendix for the whole questions.)
Reliability and Validity
MIYHS is a reliable and a standard instrument developed and validated by the
Maine CDC. Many questions in the MIYHS survey were taken from other national
surveys. Some of the questions were taken from the YRBS. The reliability and validity of
the latter were performed by the CDC using two test-retest reliability studies, one in 1992
and a second one in 2000 (CDC, 2004). In the first study, results showed that about
threefourths of the items used in the questionnaire were rated as having substantial or
higher reliability (CDC, 2004). Kappa was equal to 61%-100%, with no statistically
significant differences between the prevalence estimates for the first and second times the
questionnaire was administered. The second study result in 2000 showed that about one
of five items (22%) in the questionnaire had significantly different prevalence estimates
for the first and second times that the questionnaire was administered (CDC, 2004). In
2003, the CDC conducted a review of existing empirical literature to assess cognitive and
situational factors that might affect the validity of adolescent self-reporting of behaviors
measured by the YRBS questionnaire (CDC, 2004). The CDC determined that although
self-reports of these types of behaviors are affected by both cognitive and situational
factors, these factors do not threaten the validity of self-reports of each type of behavior
equally (CDC, 2004).

Data Analysis Plan
Because the sample collected by the MIYHS was stratified by county, public
health district, or schools, all estimates were weighted to reflect the distribution of the
variables in the middle and high school student population.
In this study, I addressed three research questions:
Research Question 1: Using the MIYHS dataset, what is the relationship between
mental health problems and substance use in youth who are MS years of age and youth
who are HS years of age?
H01: There is no relationship between mental health problems and substance use in
youth who are MS years of age and youth who are HS years of age.
Ha1: There is a relationship between mental health problems and substance use in
youth who are MS years of age and youth who are HS years of age.
To answer question 1, I used odds ratios from a logistic regression model to
determine the relationship, direction, strength, and significance between mental health
problems variables and substance use. Mental health and substance were nominal
(dichotomous). When the dependent variable is dichotomous, logistic regression model,
which gives the odds ratio, allows for adjustment of potential confounders in
multivariable analysis.
Research Question 2: Using the MIYHS dataset, what is the relationship between
mental health problems and social support in youth who are MS years of age and youth
who are HS years of age?
H01: There is no relationship between mental health problems and social support in
youth who are MS years of age and those who are HS years of age.

Ha1: There is a relationship between mental health problems and social support in
youth who are MS years of age and those who are HS years of age.
To answer question 2, I used the odds ratio from a logistic regression model to
determine the relationship, direction, strength, and significance between the mental health
variable and substance use. Mental health problems and substance will be nominal
(dichotomous). The odds ratio was used for the reasons given above.
Research Question 3: What is the relationship between substance use and social
support in youth who are MS years of age and youth who are HS years of age?
H01: There is no relationship between substance use and social support in youth
who are MS years of age and youth who are HS years of age.
Ha1: There is a relationship between substance use and social support in youth who
are MS years of age and youth who are HS years of age.
To answer question 3, I used the odds ratio from a logistic regression model to
determine the relationship direction strength and significance between mental health
variables and substance use. Mental health and substance used nominal (dichotomous).
The justification for using the odds ratio is provided in question 1 above.
Threats to Validity
The original questionnaires were tested and retested and were found to be valid
and reliable. To ensure that the design features are maintained during analysis, all
estimates were weighted to reflect the distribution of the variables in the middle and high
school student population (CDC, 2004). In 2003, the CDC conducted a review of existing
empirical literature to assess cognitive and situational factors that might affect the validity
of adolescent self-reporting of health risk behaviors measured by the YRBS questionnaire

(CDC, 2004). The CDC determined that although self-reports, health risk behaviors are
affected by both cognitive and situational factors, these factors do not threaten the
validity of self-reports of each type of behavior equally (CDC, 2004). Further details can
be found in the CDC codebook.
Ethical Procedures
This current study included analysis of secondary data; therefore, no informed
consent was needed. Authorization for use of the MIYHS was obtained from the Maine
CDC after I signed a confidentiality agreement and the Walden IRB approval was
obtained. No data access or analysis began until both the CDC and the Walden IRB
approvals were obtained.
Summary
This chapter presents the design and rationale for the current study. Using the
MIYHS survey, I analyzed the MIYHS secondary data to assess whether an association
exists between mental the variables of health problems, substance use, and social support.
For the current study, I focused on MS and HS students’ data from Maine’s public
quasi-public, and private schools from the 2017 MIYHS. To ensure that the design
features (e.g., stratification, cluster, etc) were maintained during analysis, I used
weightings consistent with the original survey results reported by the CDC to reflect the
distribution of the variables in the middle and high school student population.
Multivariable logistic regression used to assess whether an association exists between
dependent and independent variables, and this regression analysis enabled adjustment for
possible confounders. Chapter 4 will provide the study results and summary.

Chapter 4: Results
Introduction
Using secondary data from the MIYHS 2017, the purpose of my study was to
determine (a) the relationship between mental health and substance use among youth who
are MS or HS students, (b) the relationship between mental health problems and social
support in youth who are MS or HS students, and (c) the relationship between substance
use and social support in youth who are MS or HS students.
I addressed the following research questions:
Research Question 1: Using the MIYHS dataset, what is the relationship between
mental health problems and substance use in youth who are MS years of age and youth
who are HS years of age?
H01: There is no relationship between mental health problems and substance use in
youth who are MS years of age and youth who are HS years of age.
Ha1: There is a relationship between mental health problems and substance use in
youth who are MS years of age and youth who are HS years of age.
Research Question 2: Using the MIYHS dataset, what is the relationship between
mental health problems and social support in youth who are MS years of age and youth
who are HS years of age?
H01: There is no relationship between mental health problems and social support in
youth who are MS years of age and those who are HS years of age.
Ha1: There is a relationship between mental health problems and social support in
youth who are MS years of age and those who are HS years of age.

Research Question 3: What is the relationship between substance use and social
support in youth who are MS years of age and youth who are HS years of age?
H01: There is no relationship between substance use and social support in youth
who are MS years of age and youth who are HS years of age.
Ha1: There is a relationship between substance use and social support in youth who
are MS years of age and youth who are HS years of age.
Mental health problems were measured based on MIYHS items that asked
questions on sad feelings or suicidal ideation for the past 2 weeks. The items with
questions on mental health problem are as follows:
•During the past 12 months, did you ever feel so sad or hopeless almost every
day for 2 weeks or more in a row that you stopped doing some usual
activities?
•During the past 12 months, did you ever seriously consider attempting
suicide?
Social support was measured based on MIYHS items that asked questions about love and
support from family as well as communication with family and friends. These were
captured by the following two items:
1. I have a family that gives me love and support.
2. I have parents who are good at talking with me about things.
Substance use was measured based on MIYHS items that asked questions about the use
of substances. The following item captured information on substance use:
• During your life, how many times have you used any form of cocaine,
including powder, crack, or freebase.

This chapter will present data collection, study results, and a summary.
Data Collection
The Maine CDC collected data from February 2nd through February 13th, 2015, for
MS and HS youths using specific surveys developed for their respective age groups.
The MIYHS was developed and implemented in 2015 by the collaborative effort of the
Maine Department of Education and the Maine Department of Health and Human
Services, and The Pan Atlantic Research of Portland, Maine administered the 2015 Youth
Health Survey (MIYHS, 2017). Many questions in the MIYHS survey were taken from
other national surveys such as the YRBS. The reliability and validity of the YRBS
questionnaire were evaluated by the CDC using two test-retest reliability studies (CDC,
2004). The MIYHS is appropriate for this study because the variables used in the survey
contained the variables that were used in the study to assess the association between
mental health problems with social support and substance use.
Sampling Process
The CDC used stratified random sampling to obtain participants. The sampling
frame included all of Maine’s public schools, quasi-public schools, and private schools
that had about 60% of public funds. Schools with fewer than 10 students were excluded,
as were schools with alternative education and youth development centers. The sample
interval of 14.33 was computed by dividing the frame of 344 participants with the desired
sample size of 24 schools. A random number was chosen from 1 to 14.33, and a random
number was 1. Therefore, the first school was chosen, followed by every 14.33th school
rounded to the nearest integer taken. Schools that did not respond were replaced by
schools that were randomly selected from the sample interval (MIHYS, 2017). During the

data collection process, some schools were no longer eligible to participate in the survey
due to the reconfiguration of the grades or school closure. Therefore, these schools were
replaced to ensure that there was an adequate sample size and response rate.
Weighting
For this study, the pre-computed base weight and the principal sampling unit
(PSU) provided by the CDC were used. The computational details of the weight are
presented in the MIYHS methodology book (CDC, 2015). A brief outline of the method
used by the CDC for computing the weight is as follows. For the MS and HS survey, all
the schools that were eligible received an initial base weight of one (1). For the school
that participated in the MS and HS surveys, the base weight was computed to reflect the
probability of the specific version assignment. The count from summarizing the response
data was used to obtain the version probability of version assignment. For the survey
version assigned to a class, the ratio of the class version to all the classes within the
school was used. To obtain the overall probability of each version assignment, the school
probability for that version was multiplied for that class version.
The base weight for the school and class within the school version assignment
process was calculated as one divided by the assignment probability of each version.
According to the Maine CDC (2017), the version base weights were then computed as 1
divided by the product of the stage weight, that is, Base weight = 1 / mod_pM, M Є (A,
B, C, D). The computed weight, principal sampling unit, and stratification variable for
different levels of analysis were provided in the data sets by the Maine CDC. Other
methodological details are found in the codebook (MIYHS, 2015).

To gain access to the MIHYS data set, I signed a confidentiality agreement. I also
signed a data sharing and protection agreement. I obtained IRB approval from Walden
University and the Maine CDC before I commenced with the data analysis. Because this
study is a secondary data analysis, no informed consent was needed from participants.
However, I obtained authorization from the Maine CDC to use the MIYHS dataset for
analysis. Once all documentation was completed, a USB drive with single-user
passwordprotected data was sent to me by the CDC Maine.
Change in Planned Analysis
The original goal, as documented in earlier chapters, was to measure substance
use using the following questions:
•During your life, how many times have you used methamphetamines (also
called speed, crystal, crack, or ice)?
•During your life, how many times have you used ecstasy (also called
MDMA)?
However, these two questions were not in the data set I received from Maine CDC.
Therefore, to offset this data limitation, I used the following substitute question for
substance use: During your life, how many times have you used any form of cocaine,
including powder, crack, or freebase?
Data for the Current Study
For the current study, I used the dataset provided by the CDC after selecting the
specific questions needed for my analysis.
Research Question 1: Using the MIYHS dataset, what is the relationship between mental
health and substance use in youth who are MS years of age and youth who are HS years?

H01: There is no relationship between mental health and substance use in youth
who are MS years of age and youth who are HS years.
Ha1: There is a relationship between mental health and substance use in youth who
are MS years of age and youth who are HS years.
To answer Research Question 1, I used:
•Item 14: Have you ever seriously thought about killing yourself?
•Item 18: During the past 12 months, did you ever feel so sad or hopeless
almost every day for two weeks or more in a row that you stopped doing
some usual activities;
•Item 20: During the past 12 months, did you ever seriously consider
attempting suicide.
•Item 32: Have you ever used an electronic vapor product?
•Item 69: During your life, how many times have you used any form of
cocaine, including powder, crack, or freebase.
Possible confounder
•Item 85: About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs?
•Item 45: About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs?
Research Question 2: Using the MIYHS dataset, what is the relationship between
mental health problems and social support in youth who are MS years of age and youth
who are HS years of age?

H01: There is no relationship between mental health problems and social support in
youth who are MS years of age and those who are HS years of age.
Ha1: There is a relationship between mental health problems and social support in
youth who are MS years of age and those who are HS years of age.
To answer Research Question 2, I used:
•Item 18: During the past 12 months, did you ever feel so sad or hopeless
almost every day for two weeks or more in a row that you stopped doing some
usual activities;
•Item 107: I have support from adults other than my parents.
•Item 108: I have a family that gives me love and support.
Possible confounder
•Item 45: About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs?
•Item 85: About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs?
Research Question 3: What is the relationship between substance use and social
support in youth who are MS years of age and youth who are HS years of age?
H01: There is no relationship between substance use and social support in youth
who are MS years of age and youth who are HS years of age.
Ha1: There is a relationship between substance use and social support in youth who
are MS years of age and youth who are HS years of age.
To answer research question three, I used:

•Item 63: During the past 30 days, how many times did you take a prescription
drug (such as Oxycodone, Percocet, Vicodin, Codeine, Adderall, Ritalin, or
Xanax) without a doctor’s prescription?
•Item 69: During your life, how many times have you used any form of
cocaine, including powder, crack, or freebase.
Possible confounder
•Item 45: About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs?
•Item 85: About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs?
•Item 108: I have a family that gives me love and support) are included in the
construct for social support.
Statistical Analysis
After importing the data into SPSS, I cleaned the data to get it ready for analysis.
Students with sixth grade, Ungraded or other grades, or no response to grade question (In
what grade are you?) have their grade set to missing prior to analysis (per communication
with Maine CDC). I recoded some multi-category variables into two categories (yes or
no) to avoid a sparse category that might cause convergence problems. The recoded
variables are presented in Table 1. Because the sample collected by the MIYHS was
stratified by county, public health district, or schools, I applied weight to all estimates to
reflect the distribution of the variables in the middle and high school student population
in Maine. Without weighting to reflect the survey design, any analysis will be invalid.

Table 1
Recoded Items in Current Study
Items Original data response Current study recoded
categories response categories
Item 69: During your life,
how many times have you
used any form of cocaine,
including powder, crack, or
freebase?
1 = A. 0 times
2 = B. 1 or 2 times
3 = C. 3 to 9 times
4 = D. 10 to 19 times
5 = E. 20 to 39 times
6 = F. 40 or more times,
1 is recoded to 0 (None) 2
to 6 is recoded to 1 (Yes:
at least once)
Missing is recoded to
missing
Possible Confounder:
Item 85 (for HS)/ Item 45 (for
MS): About how many adults
over 21 have you known
personally who in the past
year have used marijuana,
crack, cocaine or other
drugs)?
1 = A. None
2 = B. 1 adult
3 = C. 2 adults
4 = D. 3 or 4 adults
5 = E. 5 or more adults,
1 is recorded to 0 (none)
2 to 5 is recorded to 1
(Yes)
Missing is recorded to
missing
Item 107: I have support from
adults other than my parents
1 = A. Not at all or
rarely
2 = B. Somewhat or
sometimes
3 = C. Very or
often 4 = D. Extremely or
almost always.
1 is recorded to 0 (none)
2 to 4 is recorded to 1
(Yes)
Missing is recorded to
missing
Item 108: I have a family that
gives me love and support.
1 = A. Not at all or
rarely
2 = B. Somewhat or
sometimes
3 = C. Very or
often 4 = D. Extremely or
almost always,
1 is recorded to 0
(No/rarely)
2 to 4 is recorded to 1
(Yes: I receive love and
support)
Missing is recorded to
missing
Item 63: During the past 30
days, how many times did you
take a prescription drug (such
as Oxycodone,
Percocet, Vicodin, Codeine,
Adderall, Ritalin, or Xanax)
without a doctor’s
prescription?
1 = A. 0 times
2 = B. 1 or 2 times
3 = C. 3 to 9 times
4 = D. 10 to 19
times 5 = E. 20 to 39
times
6 = F. 40 or more times.
1 is recorded to 0
(None: 0 times)
2 to 6 is recorded to 1
(Yes: at least once) Missing
is recorded to missing

I selected questions that appear on all four questionnaire versions. Because I was
interested in the analysis at all levels, the weighting, principal sampling unit, and strata
reflected this level of analysis. The reason for analysis at all levels is to ensure results can
be applied to MS and HS students in the state of Maine. The weighting variables to
reflect different levels of analysis were provided by the CDC. To prepare the data for
state-level analysis, I created a dataset with appropriate variables that reflect the complex
survey design for this chosen level of analysis. These variables include str_notschool for
the strata, psu_notschool for principal sampling unit or cluster, and wstaabcd for the
weight; these variables were provided by CDC. I applied the finite population correction
(FPC) for estimating variance under simple random sampling assumption (FPC Factor,
2008).
Because of the very large sample size (e.g., N= 35,503 for HS), the p-value for
testing association had statistical significance even when the effect (odds ratio) size
lacked practical importance. Therefore, the confidence interval was considered more
appropriate for testing hypotheses since the significance test using p-value can be
inverted to produce a confidence interval (Knapp, 2017). This is consistent with the
efforts of American Statistical Associate in discouraging widespread wrongful use of
pvalues (Wasserstein & Lazar, 2016). Using univariate and multivariable logistic
regression, I calculated the odds ratio for assessing the association between mental health
problems and social support and that between mental health problems and substance use.
I also used logistic regression to compute odds ratios for assessing the association
between social support and substance use. A reason for the multivariate logistic
regression is to assess whether the added covariate (adult over 21 that use substances)

will be a confounder of the identified association from the univariate model. This
confounding will be assessed by change in the univariate odds ratio when the variable is
added into the multivariable logistics regression model. The multivariable logistic
regression model adjusted for a response to the following item: About how many adults
over 21 have you known personally who in the past year have used marijuana, crack,
cocaine, or other drugs?
An important assumption of logistic regression is that the log odds (logit) of the
dependent variable are linearly related to the independent variable. Although
HosmerLemeshow goodness of fit test is often used for assessing goodness-of-fit for
logistic regression, this test would be inappropriate in complex surveys as weighting
invalidate the assumption of independence, identical distribution required for the
HosmerLemeshow goodness of fit test (Archer, Lameshow, & Hosmer, 2007; Shah,
Institute, & Barnwell, 2003). A goodness of fit test was based on pseudo R-square.
Analyses were performed using SPSS Version 26 premium with an add-on for complex
surveys.
Results
Demographics
In total, there are 35,503 participants for HS. Weighted data available on HS were
55,088; of these, 26,456 are female, and 28296 were male. The majority (90.0%) are
white, and least (0.1%) represented are Native Hawaiian or other Pacific Islander. Table 2
present the demographic characteristics of the participants.
Table 2

Demographics
Characteristics
HS (High School) MS (Middle School)
Actual
count
Weighted
count
% 95% CI Actual
count
Weighted
count % 95% CI
Age (years)
10 or younger
11
12 or younger
13
14
15
16
17
18 or older
N/A
N/A
160
83
5193
9359
9185
7887
3524
N/A
N/A
190
109
7354
13532
13962
13502
6439
N/A
N/A
0.3
0.2
13.3
24.6
25.3
24.5
11.7
N/A
N/A
0.3, 0.4
0.1, 0.3
12.8, 13.9
24.0, 25.2
24.8, 25.9
23.8, 25.2
11.0, 12.4
20
65
5038
9059
4153
167
18
N/A
N/A
19
89
7384
13264
6105
235
21
N/A
N/A
0.1
0.3
27.2
48.9
22.5
0.9
0.1
N/A
N/A
0.0, 0.1
0.2, 0.4)
26.0, 28.5
48.0, 49.8
21.5, 23.5)
0.7, 1.1)
0.0, 0.1)
N/A
N/A
Sex
Female
Male
17742
17395
26456
28296
48.3
51.7
47.7, 49.0
51.0, 52.3
9158
9234
13071
13871
48.5
51.5
47.6, 49.4
50.6, 52.4
Grades
7th
8th
9th
10th
11th
12th
Ungraded or
other grade
N/A
N/A
9698
9465
8636
7100
149
N/A
N/A
13681
13873
13517
13386
200
N/A
N/A
25.0
25.4
24.7
24.5
0.4
N/A
N/A
24.3, 25.8
24.7, 26.0
24.1, 25.4
23.4, 25.6
0.3, 0.5
9220
9069
N/A
N/A
N/A
N/A
63
13508
13301
N/A
N/A
N/A
N/A
82
50.2
49.5
N/A
N/A
N/A
N/A
0.3
48.5, 52.0
47.7, 51.2
N/A
N/A
N/A
N/A
0.2, 0.4
Ethnicity
Hispanic or
Latino
Yes
No
1849
32706
1500
52282
2.8
97.2
2.6, 3.0
97.0, 97.4
958
16228
668
24483
2.7
97.3
2.4, 2.9
97.1, 97.6
Table 2 continued
Demographics
Characteristics
HS (High School) MS (Middle School)
Actual
count
Weighted
count
% 95% CI Actual
count
Weighted
count
% 95% CI
Race
American Indian
951
725
1.4
1.2, 1.5
576
402
1.6
1.4, 1.8

or Alaskan
Native
Asian
Black or African
American
Hispanic Native
Hawaiian or
Other Pacific
Islander
White
Multiple Races
1133
1086
1849
95
27644
1444
984
892
1500
77
47920
1158
1.8
1.7
2.8
0.1
90.0
2.2
1.3, 2.5
1.1, 2.5
2.6, 3.0
0.1, 0.2
88.8, 91.1
2.0, 2.4
351
648
958
61
13414
942
251
455
668
43
22346
659
1.0
1.8
2.7
0.2
90.0
2.7
0.8, 1.2
1.1, 3.0
2.4, 3.0
0.1, 0.2
88.6, 91.3
2.4, 2.9
In total, there were 18,706 participants for MS. Weighted data available on MS
were 27115; of these, 13071 are female, and 13871 are male. Similar to the data for HS,
the majority of the participants in MS (90.0%) are white, and least (0.2%) represented are
Native Hawaiian or other Pacific Islander.
Answers to Research Questions
Research Question 1. Using the MIYHS dataset, what is the relationship between
mental health and substance use in youth who are MS years of age and youth who are HS
years?
H01: There is no relationship between mental health and substance use in youth
who are MS years of age and youth who are HS years.
Ha1: There is a relationship between mental health and substance use in youth who
are MS years of age and youth who are HS years.
Since the 95% confidence interval for the odds exclude one (1), I rejected the null
and conclude that the association between mental health and substance use is statistically
significant.

To answer research question # 1, I conducted a statistical analysis using odds
ratios to determine the relationship between mental health (dependent variable) and
substance use (independent variable). The results are presented below.
High school: Frequencies. Of the 26,034 weighted participants for HS,
approximately (14.7%) of the participants indicated they seriously consider attempting
suicide during the past 12 months, while 85.3% indicated not seriously consider
attempting suicide. About four percent (4.3%) of the participants indicated that they had
used cocaine, including powder, crack, or freebase, whereas 95.7% have indicated no use
of cocaine, including powder, crack, or freebase. Table 3 presents the frequency of the
participants’ responses.
Table 3
Prevalence of Mental Health and Substance Use Among HS Students
Items Actual count Weighted count Percent: 95%
CI)
Ever seriously consider attempting
suicide during the past 12 month
Yes
No
5296
29416
3827
22207
14.7
85.3
Have you used any form of
cocaine, including powder, crack
or freebase
Yes
No
860
16130
1112
24922
4.3
95.7
High school: Univariate odds ratio. The odds of seriously consider attempting
suicide during the past 12 months among participants who used any form of cocaine,
including powder, crack or freebase is 3.94 (CI: 3.36,4.61) times that of the odds among
participants who do not use any form of cocaine, including powder, crack or freebase. In
other words, the use of any form of cocaine, including powder, crack, or freebase is

associated with 293% higher odds of seriously considering attempting suicide in the past
12 months. Since the 95% confidence interval for the odds excludes one (1), the odds are
statistically significant. Table 4 presents the univariate analysis of the participants. Table
4 presents the odds ratio.
High school: Multivariable or adjusted odds ratio. Controlling for adults over 21
around participants who have used illegal substances in the past for HS, the odds of ever
seriously considering attempting suicide during the past twelve months among
participants who indicated the used of cocaine, including powder, crack or freebase is
3.057 increased in odds than among participants who indicated no use of cocaine,
including powder, crack or freebase. This suggests that the use of cocaine, including
powder, crack, or freebase, is associated with 205.7% higher odds of participants ever
seriously considering attempting suicide during the past twelve months. Table 4 presents
the adjusted odds ratio between mental health and substance use.
Table 4
Univariate and Multivariable Odds Ratio for Assessing the Association Between Mental
Health and Substance Use Among HS Students
Items
Univariate odds ratio ( 95%
CI)
Multivariable odds
ratio (95% CI)
Dependent: Ever seriously
consider attempting suicide during
the past 12 month
Have you used any form of

cocaine, including powder, crack
or freebase
Yes vs. No
3.935 (3.360, 4.608)
3.057 (2.383, 3.924)
Note. The multivariable logistic regression adjusted for the following question: About
how many adults over 21 have you known personally who in the past year have used
marijuana, crack, cocaine, or other drugs?
Middle school: Frequencies. Of the 12,961 weighted participants for MS,
approximately sixteen percent (16.5%) of the participants seriously thought about killing
them self, while 83.5% indicated no thought about killing them self. About ten percent
(10.3%) of the participants indicated ever used an electronic vapor product, whereas
89.7% have indicated no use of an electronic vapor product. The odds of participants who
thought about killing themselves is 3.692 (CI: 3.174, 4.294) times that of the odds among
MS participants who do not use an electronic vapor product. In other words, serious
thought about killing oneself in MS is associated with 269% higher odds of using an
electronic vapor product. Since the 95% confidence interval for the odds excludes one
(1), the odds are statistically significant. Table 5 presents the frequency of the MS
participants.
Table 5
Frequency of Prevalence of Mental Health and Substance use Among MS Students
Items
Actual count
Weighted
count
Percent: 95%
CI
Have you ever seriously thought about
killing yourself
Yes
No
3074
15155
2142
10820
16.5
83.5
Have you ever used an electronic vapor

product Yes
No 991
8072 1339
11622
10.3
89.7
Middle school: Multivariable or adjusted odds ratio. Have you ever seriously
thought about killing yourself (dependent variable). Have you ever used an electronic
vapor product (independent variable). The model did not converge for the MS. Table 6
presents the odds ratio and adjusted odds ratio.
Table 6
Univariate and Multivariable Odds Ratio for Assessing the Association Between Mental
Health and Substance Use Among MS Students
how many adults over 21 have you known personally who in the past year have used
marijuana, crack, cocaine, or other drugs?
Items
Univariate odds ratio (
95% CI)
Multivariable odds
ratio (95% CI)
Dependent: Have you ever
seriously thought about killing
yourself
Have you ever used an
electronic vapor product
Yes vs. No
3.692 (3.174, 4.294)
Model did not
converge
Note. The multivariable logistic regression adjusted for the following question: About

Research Question 2. Using the MIYHS dataset, what is the relationship between
mental health problems and social support in youth who are MS years of age and youth
who are HS years of age?
To answer research question # 2, I conducted a statistical analysis using the odds
ratios to determine the relationship between mental health problems (dependent variable)
and social support (independent variable).
High school: Frequencies. Of the 34,989 weighted participants for HS,
approximately twenty-six percent (26.9%) of the participants indicated feeling sad or
hopeless almost every day for 2 weeks or more in the past 12 months, while 73.1%
indicated not feeling of sad or hopeless for the same time period. About ninety-one
percent (91.9%) of the participants indicated that they have social support, while 8.1%
indicated no social support. Table 7 presents the frequency of the participants.
Table 7
Frequency of Prevalence of Mental Health and Social Support Among HS Students
Items
Actual count Weighted count Percent: 95%
CI
Feeling sad or hopeless almost
every day for two weeks or more
in the past 12 months
Yes
No
9462
24835
9417
25571
26.9
73.1
Support from adults other than
my parents
Yes
No
20985
2070
32154
2834
91.9
8.1

High school: Univariate odds ratio. The odds of feeling sad or hopeless almost
every day for 2 weeks or more in the past 12 months among participants who have
support from adults other than parents is 0.467 (CI: 0.419,0.521) times that of the odds
among participants without support from adults other than parents. In other words,
support from adults other than parents is associated with 53% lower odds of feeling sad
or hopeless almost every day for 2 weeks or more in the past 12 months. Since the 95%
confidence interval for the odds excludes one (1), the odds are statistically significant.
Table 8 presents the odds ratio.
High school: Multivariable or adjusted odds ratio. Controlling for adults over 21
around participants who have used substance in the past for HS, the odds of feeling sad or
hopeless almost every day for 2 weeks or more during the past twelve months among
participants who indicated support from adults other than parents is 0.422 times the odds
among participants who indicate no support from adults other than parents. This suggests
that support from adults other than parents is associated with 57.8% lower odds of feeling
sad or hopeless almost every day for 2 weeks or more. Table 8 presents the adjusted odds
ratio.
Table 8

Univariate and Multivariable Odds Ratio for Assessing the Association Between
Mental Health and Social Support Among HS Students
how many adults over 21 have you known personally who in the past year have used
marijuana, crack, cocaine, or other drugs?
Middle school: Frequencies. Of the 6,442 weighted participants of MS,
approximately nineteen percent (19.4%) of the participants indicate that they felt so sad
or hopeless almost every day for 2 weeks or more in a row that they stopped doing some
unusual activities, while 80.6% indicated not feeling so sad or hopeless almost every day
for 2 weeks or more in a row that they stopped doing some unusual activities. Most
(97.4%) of the participants indicated that the family gives them love and support, whereas
Items
Univariate odds ratio ( 95%
CI)
Multivariable odd ratio
(95% CI)
Dependent: Feeling sad or
hopeless almost every day
for 2 weeks or more in the
past 12 months
Support from adults
other than my parents
Yes vs. No
0.467 (0.419, 0.521)
0.422 (0.348, 0.511)
Note. The multivariable logistic regression adjusted for the following question: About

2.6% have indicated that no family gives them love and support. Table 9 presents the
frequency of the participants.
Table 9
Frequency of Prevalence of Mental Health and Social Support Among MS Students
Items
Actual count Weighted count Percent: 95%
CI
Have you ever felt so sad or
hopeless almost every day for 2
weeks or more in a row that you
stopped doing some unusual
activities
Yes
No
2036
7024
1247
5195
19.4
80.6
Family give me love and support
Yes
No
12458
435
6273
169
97.4
2.6
Middle School: Univariate Odds Ratio. The odds of feeling so sad or hopeless
almost every day for 2 weeks or more in a row that participants stopped doing some
unusual activities is 0.249 (CI: 0.170,0.364) times that of the odds among participants
who had family that give them love and support. In other words, family love and support
was associated with 75% lower odds of feeling so sad or hopeless almost every day for 2
weeks or more in a row. Since the 95% confidence interval for the odds excludes one (1),
the odds are statistically significant. Table 10 presents the odds ratio.
Middle school: Multivariable or adjusted odds ratio. Controlling for adults over
21 around participants who had used substance in the past for MS, the odds of feeling sad
or hopeless almost every day for 2 weeks or more among participants who indicated their
family gives them love and support was 0.285 times the odds among participants who

indicate their family did not give them love and support. This suggests that family love
and support are associated with 71.5% lower odds of feeling sad or hopeless almost every
day for 2 weeks or more. Table 10 presents the adjusted odds ratio.
Table 10
Univariate and Multivariable Odds Ratio for Assessing Association Between Mental
Health and Social Support Among MS Students
how many adults over 21 have you known personally who in the past year have used
marijuana, crack, cocaine, or other drugs?
Items
Univariate odds ratio ( 95%
CI)
Multivariable odd ratio
(95% CI)
Dependent: Have you ever
felt so sad or hopeless
almost every day for 2
weeks or more in a row
that you stopped doing
some unusual activities
Family give me love
and support Yes vs. No
0.249 (0.170, 0.364)
0.285 (0.191, 0.425)
Note. The multivariable logistic regression adjusted for the following question: About

Research Question 3. What is the relationship between substance use and social
support in youth who are MS years of age and youth who are HS years of age?
H01: There is no relationship between substance use and social support in youth
who are MS years of age and youth who are HS years of age.
Ha1: There is a relationship between substance use and social support in youth who
are MS years of age and youth who are HS years of age.
Since the 95% confidence interval for the odds exclude one (1), I rejected the null
and conclude that the association between substance use and social support is statistically
significant.
To answer Research Question 3, I conducted a statistical analysis using the odds
ratios to determine the relationship between mental health (dependent variable) and social
support (independent variable).
High school: Frequencies. Of the 24,779 weighted participants of HS,
approximately four percent (4.3%) of the participants indicate using any form of cocaine,
including powder, crack, or freebase, while 95.7% indicated not using any form of
cocaine, including powder, crack or freebase. About ninety-four percent (94.3%) of the
participants indicated family gives them love and support, whereas 5.7% have indicated
not having family give them love and support. Table 11 presents the frequency of the
participants.
Table 11
Frequency of Prevalence of Substance Use and Social Support Among HS Students
Items
Actual count Weighted count Percent: 95%
CI
Have you used any form of

cocaine, including powder, crack
or freebase
Yes
No
860
16130
1112
24922
4.3
95.7
Family give me love and support
Yes
No
21699
1292
23367
1412
94.3
5.7
High School: Univariate Odds Ratio. The odds of using any form of cocaine,
including powder, crack, or freebase among participants who have family that give them
love and support is 0.115 (CI: 0.095, 0.140) times that of the odds among participants
without family who give them love and support. In other words, family support is
associated with 88% lower odds of using any form of cocaine, including powder, crack,
or freebase. Since the 95% confidence interval for the odds excludes one (1), the odds are
statistically significant. Table 12 presents the odds ratio.
High School: Multivariable or Adjusted Odds Ratio. Controlling for adults over
21 around participants who have used substance in the past for HS, the odds of family
love and support among participants who indicated the used of any form of cocaine,
including powder, crack or freebase is 0.115 times the odds among participants who
indicate no used of any form of cocaine, including powder, crack or freebase. This
suggests that the use of drugs is associated with 88.5% lower odds of family love and
support. Table 12 presents the adjusted odds ratio.
Table 12
Univariate and Multivariable Odds Ratio for Assessing the Association Between Substance
Use and Social Support Among HS Students
Items Univariate odds ratio ( 95% Multivariable odds ratio

CI) (95% CI)
Dependent: Have you
used any form of cocaine,
including powder, crack
or freebase
Family give me love
and support Yes vs. No
0.115 (0.095, 0.140)
0.115 (0.083, 0.160)
Note. The multivariable logistic regression adjusted for the following question: About
how many adults over 21 have you known personally who in the past year have used
marijuana, crack, cocaine, or other drugs?
Middle school: Frequency. Of the 18,693 weighted participants of MS,
approximately one percent (1.4%) of the participants indicate during the past 30 days
took a prescription drug (such as Oxycodone, Percocet, Vicodin, Codeine, Adderall,
Ritalin, or Xanax) without a doctor’s prescriptions, while 98.6% indicated during the past
30 days not a prescription drug (such as Oxycodone, Percocet, Vicodin, Codeine,
Adderall, Ritalin, or Xanax) without a doctor’s prescriptions. About ninety-seven percent
(97.4%) of the participants indicated family gives them love and support, whereas 2.6%
have indicated not having family give them love and support. Table 13 presents the
frequency of the participants.
Table 13
Frequency of Prevalence of Substance use and Social Support Among MS Student
Items
Actual count Weighted count Percent: 95%
CI
Family give me love and support
Yes
No
12458
435
6273
169
97.4
2.6
During the past 30 days, did you
take a prescription drug (such as
Oxycodone, Percocet, Vicodin,
Codeine, Adderall, Ritalin, or

Xanax) without a doctor’s
prescriptions
Yes
No
275
17212
259
18434
1.4
98.6
Middle School: Univariate Odds Ratio. The odds of taking a prescription drug
(such as Oxycodone, Percocet, Vicodin, Codeine, Adderall, Ritalin, or Xanax) without a
doctor’s prescription during the past 30 days is 0.124 (CI: 0.084, 0.182) times that of the
odds among participants who have family that give them love and support. In other
words, family love and support are associated with 88% lower odds of taking a
prescription drug (such as Oxycodone, Percocet, Vicodin, Codeine, Adderall, Ritalin, or
Xanax) without a doctor’s prescription during the past 30 days. Since the 95% confidence
interval for the odds excludes one (1), the odds are statistically significant. Table 14
presents the odds ratio.
Middle School: Multivariable or Adjusted Odds Ratio. Controlling for adults
over 21 around participants who have used substance in the past for MS, the odds of
using prescription drugs among participants who indicated their family gives them love
and support is 0.122 times the odds among participants who indicate their family did not
give them love and support. This suggests that family love and support are associated
with 87.8% lower odds of using prescription drugs. Table 14 presents the adjusted odds
ratio.
Table 14
Univariate and Multivariable Odds Ratio for Assessing the Association Between Substance
Use and Social Support Among MS Students
Items
Univariate odds ratio ( 95%
CI)
Multivariable odds ratio
(95% CI)

Dependent: During the
past 30 days, did you take
a prescription drug (such
as Oxycodone, Percocet,
Vicodin, Codeine,
Adderall, Ritalin, or
Xanax) without a doctor’s
prescriptions
Family give me love
and support Yes vs. No
0.124 (0.084, 0.182)
0.122 (0.061, 0.244)
Note. The multivariable logistic regression adjusted for the following question: About
how many adults over 21 have you known personally who in the past year have used
marijuana, crack, cocaine, or other drugs?
Summary
This chapter presents the result of the study. Using the MIYHS survey, the study
assessed whether an association exists between mental health problems, substance use,
and social support. Chapter 4 presents the participant’s demographics, data collection,
study results, and summary.
The study focuses on MS and HS students in all Maine’s public schools and quasi-
public schools and private schools that have about 60% of public funds. The majority of
the participants were white. The original survey used stratified random sampling to select
participants; this ensures that the participants are selected proportionate to the number of
participants in Maine. Many questions in the MIYHS survey were taken from other
national surveys, including the YRBS. The questionnaires were tested and retested and
were found to be valid and reliable. To ensure that the design features are maintained
during analysis, all estimates were weighted to reflect the distribution of the variables in

the middle and high school student population. Multivariable logistic regression was used
to assess whether an association exists between dependent and independent variables, and
this regression analysis enables adjustment for possible confounders. The result shows
that there is a statistically significant association between mental health and substance
use, mental health and social support, substance use and social support.
Chapter 5 will provide the study overview, including the findings, limitations,
recommendations, implications, and the potential for future research.
Chapter 5: Discussion, Conclusions, and Recommendations
Using secondary data from the MIYHS 2017, the purpose of my study was to
determine (a) the relationship between mental health problems and substance use among
youth who are MS or HS students, (b) the relationship between mental health problems
and social support in youth who are MS or HS students, and (c) the relationship between
substance use and social support in youth who are MS or HS students.
For my dissertation, I used a cross-sectional, retrospective design using data from
the MIYHS. I adopted the same definitions used by the MIYHS. The definitions and
supporting questions are listed below. Mental health problem was measured as a sad
feeling or suicidal ideation for the past 2 weeks. Social support was measured by love and
support from family as well as communication with family and friends. These are
captured by the following two questions: (a) I have a family that gives me love and
support (b); I have parents who are good at talking with me about things. In this survey,
substance use was measured using the following question:
• During your life, how many times have you used any form of cocaine,
including powder, crack, or freebase.

Chapter 5 provides an overview of the study, which includes the interpretation of
findings, limitations of the study, recommendations, implications, and conclusions. I will
also describe how the results of the study may help with positive social change. I used the
MIYHS secondary data to obtain the result for the study. These data were collected by the
Maine CDC using the MIYHS. Mental health problems are associated with substance use
and social support.
Interpretation of Findings
The study findings are presented in the context of the literature review on mental
health association with substance use and social support. The findings indicate that
mental health has been a major public health concern that needed further examination
among youths. In the current study, I focused on the association between mental health
problems, social support, and substance use among MS and HS students. The analysis
was conducted using SPSS version 25 for assessing the following questions:
Mental Health
•Item 14: (Have you ever seriously thought about killing yourself)?
•Item 18: (During the past 12 months, did you ever feel so sad or hopeless
almost every day for two weeks or more in a row that you stopped doing some
usual activities)
•Item 20: (During the past 12 months, did you ever seriously consider
attempting suicide).
Substance Abuse
•Item 32: (Have you ever used an electronic vapor product)?

•Item 45: (About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs)?
•Item 63: (During the past 30 days, how many times did you take a prescription
drug (such as Oxycodone, Percocet, Vicodin, Codeine, Adderall, Ritalin, or
Xanax) without a doctor’s prescription?
•Item 69: (During your life, how many times have you used any form of
cocaine, including powder, crack or freebase),
•Item 85: (About how many adults over 21 have you known personally who in
the past year have used marijuana, crack, cocaine, or other drugs)?
Social Support
•Item 107: (I have support from adults other than my parents).
•Item 108: (I have a family that gives me love and support).
Theoretical Framework
Chapter 2 described mental health problems and the association with substance use
and social support among young adults. Two conceptual frameworks were used in this
study: The relation regulation theory and self-medication theory. The self-medication
theory helps to better understand factors that make individuals to use substance. This
theory is based on the idea that an individual’s use of drug is due to an untreated
underlying problem, which could be an underlying mental health problems in the context of
this study. The self-medication is in the context of regulation, where an individual’s sense
or understanding of regulation matches self-medication. The second conceptual framework
is relational regulation theory, which helps to better understand social support with mental
health problems. The idea behind RRT is that the association between social support and

mental health problems originates from people regulating their emotions through shared
activity and conversation.
The results from this study suggest that the use of any form of cocaine, including
powder, crack, or freebase, is associated with higher odds of seriously considering
attempting suicide in the past 12 months among youths. The results of this study also
suggest that using an electronic vapor product is associated with higher odds of serious
thought about killing oneself. These findings are consistent with previous literature that
showed that substance use may be associated with a mental health problem such as
suicide (Mason et al., 2014). The association between mental health and substance use
can be explained using the self-medication theory. The self-medication theory proposes
that the use of drug among youths can lead to mental health problems (Duncan, 1974a).
Substance use is a problem worldwide, and it is a risk factor for many health problems.
Considering the association between substance use and mental health, there is a need to
implement programs and policies that discourage substance use among youths.
The current study finds that support from adults other than parents is associated
with lower odds of feeling sad or hopeless almost every day for 2 weeks or more in the
past 12 months among youths. These findings are consistent with previous literature that
stated that providing social support in the family and the community helps decrease
distress and promote hope (Holden et al., 2015). However, the current study focused on
youth, whereas previous research focused on adulthood. The association between mental
health and social support can be explained using RRT. This theory states that individuals

improve their mental health through the diversity of relationships (John & Louise, 2013),
and social support is an example of diversity of relationships.
In this current study, the results show that family support is associated with lower
odds of substance use including any form of cocaine, including powder, crack, or
freebase. The result of this study also suggests that family love and support are associated
with lower odds of taking a prescription drug (e.g., Oxycodone, Percocet, Vicodin,
Codeine, Adderall, Ritalin, or Xanax) without a doctor’s prescription. These findings are
consistent with previous literature that suggests that college students with no positive
social networks are at higher risk for using a substance, including alcohol, tobacco, and
marijuana. Support from spouse and family may be protective to prevent substance use
(Mason et al., 2014; Studer et al., 2017). This study extends the body of knowledge about
association between social support and substance use because the current study focused
on youth, whereas previous studies focused on college students and older adults. The
RRT and the self-medication theory may be used to explain the association between
social support and substance use.
Limitations of the Study
This is a descriptive, correlational, cross-sectional study that measures the
association between mental health with substance use and social support in youths
between the ages of MS and HS years. The identification of association does not mean
there is causation between the variables (Seema, 2018). This is a limitation because there
might be other possible explanations for any observed association. For example, an
unknown genetic factor may be associated with mental health, and the same genetic
factor may associate with substance use. Therefore, the observed association might be

due to an unknown confounding factor. To address the limitation of confounding factors,
the study controlled for covariates that may be associated with independent and
dependent variables, for example, social, economic status, and family composition. There
may be bias due to self-reporting because the participants may forget, deceive, or may not
understand the questions, which may lead to underreporting or overreporting (Maine
CDC, 2017). Nonetheless, studies have shown that surveys completed by young adults
could provide valid and reliable information that is needed for research (Maine CDC,
2017).
Recommendations
Because the study used a cross-sectional, retrospective, correlational design,
longitudinal and cohort studies are recommended for future study with the MS and HS
population. The study focused on the analysis of the MS and HS students’ data from the
MIYHS. The study was focused on MS and HS students in Maine. A future
crosssectional study with other states is recommended to compare the study results. The
literature review showed that mental health problems associated with social support and
substance use was reported in different countries and states, such as American Indians
from the Eastern Tribe (Ni et al., 2017), Oru camp near Ago-Iwoye in Ogun state (Amosu
et al., 2016).
Based on the study results, mental health problems are associated with substance
use and social support among MS and HS students. It is recommended that early social
support may help prevent mental health problems in adulthood (Holden et al., 2015). It is
also recommended that practitioners develop focused age-specific interventions for

students at risk for mental health conditions secondary to drug use and to plan prevention
programs for school-aged youths.
Implications
The study has the potential to bring about positive social change by using the
result of the analysis to help practitioners develop focused age-specific interventions for
students at risk of mental health conditions secondary to drug use and to plan prevention
programs for school-aged youths. Mental health problems and substance use are
associated with social support. Therefore, individuals who have compromised social
support such as family and friends may experience the consequence of substance use that
may affect their well-being (Staton et al., 2007). The information from this study will add
to the existing body of knowledge on how the prevention of substance use and the
promotion of social support could improve mental health outcomes and promote positive
social change.
By identifying mental health problems early in a young person’s life, intervention
may be implemented early, thus helping the youth with mental health problems become
more productive members of the society (Costello, 2016), and thereby promoting positive
social change. According to the University of Minnesota (2016), social support can
enhance the quality of an individual’s life by providing a buffer in times of crisis. The
information from this study could help in revising and establishing programs and using
strategies that reflect community needs and monitoring outcomes. The results could be
used to identify the strengths and challenges facing young people in society (MIYHS,

2017). Early intervention will help the youth live a more productive life and avert future
negative effects of mental health problems, including the cost of hospitalization and
youth inflicting harm on themselves (Costello, 2016).
Conclusions
Previous studies have shown an association between mental health problems,
social support, and substance use. Individuals who have compromised social support such
as family and friends may experience the consequence of substance use that may affect
their well-being. However, this study showed that identification of mental health
problems early in a young person’s life, intervention may be implemented early to help
youth become more productive in society. Findings from the study showed that lack of
social support might lead to substance use and affect the well-being of MS and HS youth.
Future research in a different state is needed in validating the finding of the study and
more research on mental health problems associated with substance use and social
support should be conducted in the future.

