


NURSING I UNIT 1-lecture notes
Introduction:
COURSE CONTENT:
UNIT (1): CONCEPT AND TERMS IN MEDICAL SURGICAL
Nursing Concepts in Medical/Surgical Nursing/Rehabilitation Holistic care.
Primary Nursing
Team Nursing
Health – illness Adaptation, homeostasis, and stress
Behavior in illness
Stress/process of rehabilitation (role of the family, community, and government)
DEFINITION OF TERMS
i) Nursing:
Nursing encompasses autonomous and collaborative care of individuals of all ages, families, groups, and
communities, sick or well and in all setÝngs.
Nursing includes the promotion of health, prevention of illness, and the care of ill, disabled and dying people.
Advocacy, promotion of a safe environment, research, participation in shaping health policy and in patient and
health systems management, and education are also key nursing roles. (ICN, 2002)
ii) Nurse
is a person who has completed a program of basic, generalized nursing education and is authorized by the
appropriate regulatory authority to practice nursing in his/her country.
Basic nursing education is a formally recognized programme of study providing a broad and sound foundation in
the behavioral, life, and nursing sciences for the general practice of nursing, for a leadership role, and for post-
basic education for specialty or advanced nursing practice.
Functions of a nurse:
(1) To engage in the general scope of nursing practice, including the promotion of health, prevention of illness,
and care of physically ill, mentally ill, and disabled people of all ages and in all health care and other community
setÝngs.
(2) To carry out health care teaching.
(3) To participate fully as a member of the health care team.

(4) To supervise and train nursing and health care auxiliaries.
(5) To be involved in research.
iii) Primary nursing:
Is a nursing system in which all nursing care for a patient is managed by one nurse for a 24-hr period. Primary
nursing includes scheduling of activities, tests, and procedures etc.
Primary care nursing is when a single nurse is identified as the point of contact and primary caregiver for a
patient during his or her hospital stay or other episode of care.
The primary care nursing team is composed of that lead nurse, who directly supervises the engagement of a
licensed practical nurse and/or nursing assistant in that patient’s care. Further, the primary care nurse acts as
care partner, serving as communications liaison between the patient and his or her doctor and other care team
members. (In many facilities and systems, the position of nurse practitioner has been created to fulfill this role.)
Team-based nursing: Pairing nurses for individual patient care
Modular nursing: Like the team-based approach, where the unit is divided into quadrants and teams are
assigned to each.
Functional nursing: Nurses are each assigned specific care tasks and have a single-source direct report nurse.
Float nursing: Nurses move from unit to unit on a set schedule, or are stationed in a permanent float pool
Each has its adherents, and each can and should be evaluated to see if it would work in the healthcare setÝng
under review.
iv) Team Nursing
Team nursing is a model in which a group of healthcare professionals, including nurses, care for a group of
patients in the acute care or inpatient setÝng. Acute care, also known as critical care, is when nurses help
patients confronting life-threatening issues. This model came about in the 1950s and 1960s in a response to the
increasing shortage of nurses due to World War II and nurses leaving hospitals.
The team usually consists of a charge nurse or team leader (also a nurse), more nurses, and patient care
technicians or nurse's aides.
The charge nurse is responsible for assigning patients to the team members, as well as being knowledgeable
about the patients and their plans of care.
The nurses who are assigned to the patients’ delegate tasks to the patient care technicians or nurse's aides
within their scope of practice to assist in the care of the patients.
Each team is responsible for five to six patients, depending upon the setÝng and stafÏng.
If you've ever been a patient in a hospital, you may have had two people caring for you at a time (a nurse and a
patient care technician, or nurse's aide) each performing certain types of tasks in order to complete orders from
the healthcare provider and help you recover from illness or injury. This is considered team nursing.

Advantages of Team Nursing
Every member of the team brings something important to patient care in the team nursing model. The working
shift is started out with a conference involving the team leader or charge nurse, assigned nurse, and patient
care technician or nurse's aide. During this conference, the team discusses the patients and their plans for care.
Some of the advantages include:
1. The strengths of all healthcare professionals are utilized to provide the best care possible.
2. Each patient receives individualized care, which has been shown to improve patient outcomes and
patient satisfaction.
3. Each team member can perform the skills at which they excel, which helps with job satisfaction and
patient safety. This also provides the nurse with time to document care in the health record.
4. The patients are given the most comprehensive care and every member of the team can contribute to
decision making.
5. Have you worked on a team where every member contributed, participated, and completed the task in
a timely manner? It was a great feeling, wasn't it? Imagine being a patient on a team nursing floor
where all the members of the healthcare team contributed, participated, and met your every need.
The disadvantages of Team Nursing:
Team nursing can also be challenging because communication and delegation are necessary with this model. In
contrast with the primary nursing model, where a single nurse maintains patient care, the assigned nurse in the
team model delegates tasks to the patient care technician or nurse's aide such as performing vital signs,
bathing, drawing blood, performing ECGs, and other such skills within their scope of practice.
Some of the disadvantages include:
1. The nurse remains responsible for the duties being performed without performing them personally.
This takes time away for the nurse from the assigned patients.
2. Assigning staff with this model can be challenging, because the staff competencies must meet the
patient's needs.
3. All members of the team must also be focused on the patient and his or her needs.
HEALTH – ILLNESS ADAPTATION, HOMEOSTASIS, AND STRESS
The World Health Organization as “a state of complete physical, mental, and social well-being,defines health
not merely the absence of disease and infirmity.
Illness is a broad term that defines the poor state of mind, body, and, to a certain extent, spirit. It is the general
feeling unwell, and the body is unable perform normal function. It is an ailment that affects one’s mind and
body.
The word is used from society’s point of view on any condition that might not be a medical condition.sickness
It also means being affected by the sense of discomfort where a person assume sick roles can perform activities.
Disease is an ‘illness or sickness characterized by specific signs or symptoms.
is a particular abnormal condition that negatively affects the structure or function of all or part of an organism,
and that is not immediately due to any external injury.
Stress is the way human beings react both physically and mentally to changes, events, and situations in their
lives. People experience stress in different ways and for different reasons. The reaction is based on your
perception of an event or situation. If you view a situation negatively, you will likely feel distressed—
overwhelmed, oppressed, or out of control. For example loss of loved ones, sickness etc.
Health and wellness combine to form a state of optimal physical functioning and a feeling of emotional and
social contentment. Wellness involves the ability to adapt emotionally and physically to a changing state of
health and environment.
Illness is an altered level of functioning in response to a disease process.
Disease is a condition that results in the physiological alteration in the composition of the body.
Aspects of health and wellness
Physical – able to perform activities of daily living
Emotional – adapts to stress; expresses and identifies emotions
Social – interacts successfully with others
Intellectual – effectively learns and disseminates information
Spiritual – adopts a belief that provides meaning to life
Occupational – balances occupational activities with leisure time
Environmental – creates measures to improve standards of living and quality of life
Desired outcomes are to obtain and maintain optimal state of wellness and function which can be achieved
through health education and positive action (smoking cessation, weight loss, seeking health care)
Illness
Response to disease may be influenced by:
Assignment 1:
a) Give difference between health and illness
b) Mention 3difference between illness and sickness
c) Briefly describe homeostasis of diabetes patient

Degree of physical changes because of the disease process.
Perceptions by self and others of the disease, which may be influenced by various reliable and
unreliable sources of information, such as friends, magazines, TV, and the Internet.
Cultural values and beliefs.
Denial or fear of illness.
Social demands, time constraints, economic resources, and health care access
Adaptive Homeostasis is the temporary expansion or contraction of the homeostatic range in response to
exposure to sub-toxic, non-damaging, signaling molecules or events, or the removal or cessation of such
molecules or events (Davies, 2016).
Adaptive homeostasis enables biological systems to make continuous short-term adjustments for optimal
functioning despite ever-changing internal and external environments. Initiation of adaptation in response to an
appropriate signal allows organisms to successfully cope with much greater, normally toxic, stresses. These
short-term responses are initiated following effective signals, including hypoxia, cold shock, heat shock,
oxidative stress, exercise-induced adaptation, caloric restriction, osmotic stress, mechanical stress, immune
response, and even emotional stress.
BEHAVIOR IN ILLNESS & STRESS/PROCESS OF REHABILITATION
Illness behavior refers to “the way in which symptoms are perceived, evaluated, and acted upon by a person
who recognizes some pain, discomfort, or other signs of organic malfunction.
The Sociologist, David Mechanic, also defined illness behavior as “the ways in which given symptoms may be
differently perceived, evaluated and acted (or not acted) upon by different kinds of persons (Mechanic, 1962)”.
It refers to any behavior undertaken by an individual who feels ill to relieve that experience or to define the
meaning of the illness experience.
However, it is important to note that the study of illness behaviour is therefore the study of behaviour in its
social context (which describes how people respond to their symptoms), rather than in relation to a
physiological or Pathological condition.
STAGES OF ILLNESS EXPERIENCE
Edward Suchman (1965) devised an orderly approach for studying illness behaviour which are
(1) symptom experience.
(2) assumption of the sick role
(3) medical care contact

(4) dependent patient role
(5) recovery and rehabilitation
Each stage involves major decisions that must be made by the individual that determine whether the sequence
of stages continue or the process is discontinued.
1.Symptom Experience
Symptoms are viewed as the manifestation of bodily malfunction. It enable a person to report self-experiences
of health on a day-to-day basis
Certain etiologies such as those found in biomedicine maintain that disease occurs when an external pathogen
enters the body and disrupts physiological homeostasis. Therefore, symptoms are not believed to be part of the
―patient ‘s concept of his intact body.
In non-traditional health care systems, symptoms are believed to be manifestations of the intrusion of the
supernatural. On the other hand, non-western ideologies explain disease causation as an object intrusion, spirit
intrusion, an act of witchcraft, or the result of soul loss or neglected/transgressed social taboos (Low 1985).
Importance of Symptoms Experienced
a)The symptom is regarded as a vital part of the illness experience because it offers insight into the physiological
and psychological aspects of the patient‘s body. In this way, the symptom symbolizes the roots of a tree,
anchoring a societal understanding of medical knowledge and healing aetiologies.
b)The concept of feelings, in the form of symptoms, are important because they often act as threads that bind
the aspect of health to the personal concept of human emotion. The way an individual feels is a ―prime
criterion of health, illness, and recovery‖ (Telles and Pollack 1981).
c) Symptoms add clarity to the complex ideas of sickness and healing in such a way that it is difÏcult to discuss
either process without touching on these symbols.
2.Assumption of The Sick Role
The sick role, one of the most fundamental concepts in medical sociology, was first introduced by Talcot
Parsons in a 1948 journal article but elaborated in his 1951 book, The Social System.
When one is ill, one does not simply exit normal social roles to enter a type of social vacuum; rather, one
substitutes a new role – the sick role – for the relinquished, normal roles.
The sick role and sick-role behaviour could be seen as the logical extension of illness behaviour to complete
integration into the medical care system.
Sick role
The sick role is, “ characterized by certain exemptions, rights, and obligations, and shaped byalso a social role,
the society, groups, and cultural tradition to which the sick person belongs.

Within the context of social control responsibilities of medicine, society allows two explicit behavioral
exemptions for the sick person but also imposes two explicit behavioral requirements. The exemptions are:
1) The sick person is temporarily excused from normal social roles. The physician’s endorsement is required so
that society can maintain some control and prevent people from lingering in the sick role.
2. The sick person is not held responsible for the illness. Society accepts that cure will require more than the
best efforts of the patient and permits the patient to be “taken care of” by health care professionals and others.
In order to be granted these role exemptions, however, the patient must be willing to accept the following two
obligations:
1. The sick person must want to get well. The patient must not get so accustomed to the sick role or enjoy the
lifting of responsibilities that motivation to get well is surrendered.
2. The sick person is expected to seek medical advice and cooperate with medical experts. If a patient fails to
seek medical atention, the society and family may loose patience and sympathy for such individual.
3.Medical Care Contact
This is described as the point at which an individual sought professional medical care.
Three factors that influence the decision to seek care:
1. The background of the patient. Factors such as age, gender, race and ethnicity, and social class can
affect s health seeking behavior.
Culture: culture defines the seriousness atached to an illness as well as the action to be taken
Social class: people at the upper social class are more likely to report illness and seek medical atention
then people of lower social class due to lack of necessary resources in the later
Stress: people under stress do not tolerate illness as much as those who are not stressed
Age: older people tolerate illness more than the younger ones because they atribute illness to old age
Gender: women are seen as weaker sex and are culturally accepted to report illness more frequently
than men
Personality: personality difference make some people to exaggerate symptoms and other to minimize
them
2. The patient’s perception of the illness.
Social trigger that influences the judgment that the symptoms need professional health care:
(a)Perceived interference with vocational or physical activity, especially work related activity;‐
(b)Perceived interference with social or personal relations.
(c) A temporalizing of symptomatology (setÝng a deadline—if I’m not beter by Monday, I’ll call the
doctor);

(d) Pressure from family and friends.
3. Even for pain that may relate to a serious condition, situational factors mater.The social situation.
Symptoms that begin during the week, rather than on the weekend, are more likely to motivate prompt contact
with a physician, as do symptoms that appear at work and symptoms that appear when other people are
present.
STAGE 4: DEPENDENT PATIENT ROLE‐
With the onset of the dependent patient role, ‐the patient is expected to make every effort to get well. Some
people, of course, enjoy the benefits of this role (e.g., increased atention and escape for work responsibilities)
and atempt to malinger.
Major concerns people have during stage 4:
•1. Patients may be concerned that their illness will progressImpairments of personal cognitive functioning.
to a point that their cognitive functioning ability may be impaired and probably have memory loss,
reasoning ability, and capacity for communication.
•2. Reliance on others may be a devastating thought—because of theLoss of personal independence.
inconvenience and, in a larger sense, the idea of becoming a burden on others.
•3. For patients whose illness creates any dramatic alteration in physical image, aChanges in body image.
major readjustment may be needed.
•4. Withdrawal from key social roles. Because so many people derive their identity from their
work/occupation, any disruption in work patern or work accomplishment is very threatening. If
remuneration is affected, an extra emotional burden is created.
•5. Any chronic or serious acute condition creates questions about the patient’s future and theThe future.
extent to which there will be further incapacitation or physical or mental limitation, questions about
financial indebtedness, and questions about permanent losses in daily activities.
Stage 5: Recovery and Rehabilitation
The final stage varies depending on the type of illness. For acute patients, the process is one of
relinquishing the sick role and moving back to normal role obligations. For chronic patients, the extent to
which prior role obligations may be resumed ranges from those who forsake the sick role to those who will
never be able to leave it.
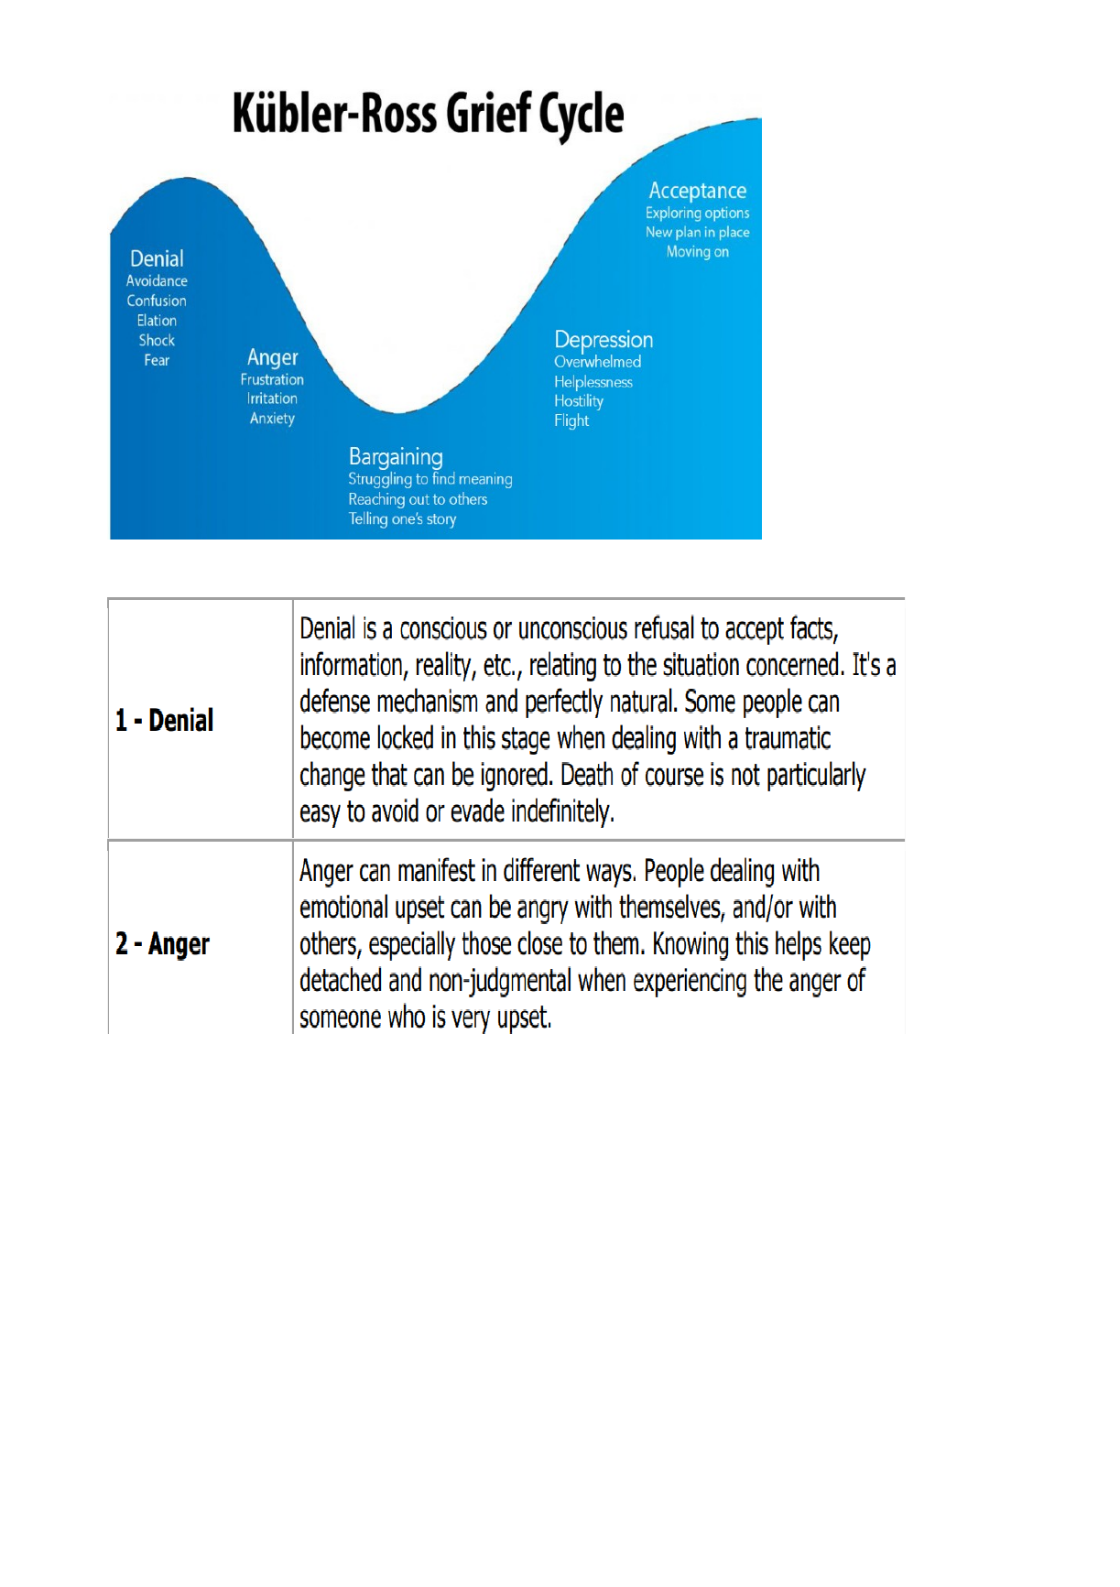
KUBLER ROSE

Family support during sickness:
The more you know about your loved one’s illness, the beter for your relative, your family and yourself.
Family members who understand a relative’s illness find that they gain a measure of control over their own
lives. In addition, sharing their concerns and experiences with others is an empowering experience with far-
reaching, positive effects.

1) The Family as Caregivers
Family act as a primary caregivers or partners in care in both the hospital and the community.
Families are generally deeply involved with their ill relative, but their insights and particular needs have
often been overlooked.
The atÝtude of the ill person determines the level of family involvement. Family members need to
understand how their behaviour toward their relative can either be supportive or detrimental.
2) Family must Know and understand the System
Families must know how to be effective in getÝng help for a seriously ill relative. They need to know what
questions to ask, whom to see, and especially where to go when they feel overwhelmed and discouraged.
As a primary care giver, family must have detailed information about their relative, they system and how to
interact with the system.
3) Family as an advocate
Family needs to be familiar with Legal Services / Legal Aid. It is occasionally necessary for families to seek
legal advice.
Aside the medico-legal issue, family must be aware of family law, health law, juvenile law, criminal law,
landlord/tenant rights, employment law and the right to employment insurance or welfare.
Family must be ready to advocate for their members at all time
4) Family as a Supporter
Families must at all times support their members physically, financially, spiritually and psychologically.
Even if treatment is refused, it is very important that family members have access to information and
support services.
Complementary and Alternative Medicine
Complementary and Alternative Medicine (CAM) is the use of treatments that are not commonly practiced
by the medical profession
i)Faith Healing
This is the use of suggestions, power and faith in God to achieve healing.
Faith healing can be:
Self-treatment through prayer.
Treatment by a lay person thought to be able to communicate with God.
Treatment by an ofÏcial church leader for whom healing is only one of many tasks.

Healing obtained from a person/ religious leader or group of persons who practice healing fulltime
without afÏliation with a major religious organization.
Others
Aromatherapy
Aromatherapy is the use of aromatic oils for relaxation.
Acupuncture
Acupuncture is an ancient Chinese technique of inserting fine needles into specific points in the body to ease
pain and stimulate bodily functions.
Homeopathy
Homeopathy is the use of micro doses of natural substances to boost immunity.
Naturopathy
Naturopathy is based on the idea that diseases arise from blockages in a person‘s life force in the body and
treatments like acupuncture and homeopathy are needed to restore the energy flow.
Aryuveda
This is an Indian technique of using oil and massage to treat sleeplessness, hypertension and indigestion.

