



Chapter 11: Care of Patients with Fluid and Electrolyte Balance
Hypervolemia
S/S: pitting edema, increased HR/BP/HR, distended neck and hand veins, weight gain, SOB, lung crackles,
pale/cool skin, decreased lab values, altered LOC
Treatment: patient safety (assess every 2 hours for PE), assess for skin breakdown (skincare), provide
supplemental O2 and position patient in semi- to improve SOB, furosemide, fowler’s fluid restriction,
monitor daily weight and output, restrict Na/low sodium diet (water follows)
Hypovolemia
S/S: increased HR, orthostatic hypotension (increased risk for falls), weak/thready pulse, flattened
neck/hand veins, increased RR, decreased turgor, warm/dry skin, dry mucous membranes, fever,
decreased urine and increased concentration, increased lab values
Treatment: fluid replacement (monitor pulse rate/quality and urine output of 30 ml/hr. during
rehydration), antidiarrheals, antiemetics, antipyretics
Calcium: Hypercalcemia
Causes: hyperparathyroidism/hyperthyroidism, dehydration, use of thiazide diuretics, use of
glucocorticoids, kidney failure, malignancy, excessive intake of calcium or vitamin D
S/S: (EKG CHANGES FROM CLOT): cyanosis, pallor, EKG changes, increased risk for blood clots, profound
muscle weakness, decreased DTR, decreased peristalsis/bowel sounds, constipation, kidney stone
formation
Calcium: Hypocalcemia
Causes: lactose intolerance, Crohn’s disease, celiac disease, acute pancreatitis, ESKD, diarrhea, wound
drainage, alkalosis (hyperventilation), hyperproteinemia
S/S: (HYPERACTIVE CRAMPS): muscle spasms ("Charley horses"), , hyperactive reflexes, + tetany
Trousseau's and Chvostek's signs, arrhythmias, weak/thready pulse, painful abdominal cramping,
diarrhea, loss of bone density (osteoporosis), brittle/fragile bones (may break with slight trauma),
confusion
Normal Calcium (Ca+): 9.0-10.5mg/dL
Potassium: Hypokalemia
Causes: diuretics, alkalosis (hyperventilation), TPN, NPO, Cushing’s syndrome, vomiting, wound drainage,
prolonged NG suctioning, heat-induced/excessive diaphoresis, corticosteroids, increased aldosterone
S/S: (SLOW, LOW, + LETHAL): low/shallow respirations, muscle weakness, reduced DTR, leg cramps, limp
muscles, lethal cardiac changes, low BP and HR, increased urine output, decreased bowel sounds
(constipation)
Normal Potassium (K+): 3.5-5.0 mEq/L
Magnesium: Hypomagnesemia
S/S: (HYPERACTIVE TWITCHING/SEIZING): HTN, dysrhythmias, constipation, , hyperactive DTRs
involuntary movements, + Trousseau’s and Chvostek’s signs, Torsade’s de Pointes, weak respirations
Normal Magnesium (Mg+): 1.8-2.6 mEq/L
Sodium: Hyponatremia
S/S: (SALT LOSS): , trouble concentrating, seizures, stupor, confusion muscle weakness/spasms,
diminished DTRs, abdominal cramping, increased urine output, loss of appetite, shallow respirations,
orthostatic hypotension, diarrhea
Normal Sodium (Na+): 136-145 mEq/L
Chapter 12: Care of Patients with Problems of Acid-Base Balance
ABG Interpretation
1. Is the pH out of range? (in range and opposite direction-fully compensated; out of range and opposite
direction-partially compensated; same direction-uncompensated)
2. Is the PaCO2 normal/out of range? (respiratory)
3. Is the HCO3 normal/out of range? (metabolic)
4. Match the one (PaCO2 or HCO3) that is the same as the pH. (acidosis or alkalosis)
5. Does the one that does not match/remains go in the opposite direction of pH? (Compensation)
6. Are PaO2 and O2 sat out of range? (hypoxemia)
Respiratory Acidosis/Metabolic Acidosis
Interpretation: Kussmaul breathing, hyperkalemia, warm/dry/pink skin
Causes: hypoventilation, asthma, COPD, pneumonia, in the table below
Respiratory Alkalosis/Metabolic Alkalosis
Interpretation: hypocalcemia and hypokalemia, dizziness, twitching, tingling, increased HR and RR
Causes: in the table below
Common Causes of Alkalosis
Metabolic Alkalosis
Increase of base components
Oral ingestion of bases:
Antacids
Parenteral base administration:
Blood transfusion
Sodium bicarbonate
Total parenteral nutrition
Decrease of acid components
Prolonged vomiting
Nasogastric suctioning
Hypercortisolism
Hyperaldosteronism
Thiazide diuretics
Respiratory Alkalosis
Excessive loss of carbon dioxide
Hyperventilation, fear, anxiety
Mechanical ventilation
Salicylate toxicity
High altitudes
Shock
Early-stage acute pulmonary problems
Common Causes of Acidosis
Metabolic Acidosis
Overproduction of hydrogen ions
Excessive oxidation of fatty acids:
Diabetic ketoacidosis
Starvation
Hypermetabolism:
Heavy exercise
Seizure activity
Fever
Hypoxia, ischemia
Excessive ingestion of acids:
Ethanol or methanol intoxication
Salicylate intoxication
Under-elimination of hydrogen ions
Kidney failure
Underproduction of bicarbonate
Kidney failure
Pancreatitis
Liver failure
Dehydration
Over-elimination of bicarbonate
Diarrhea
Respiratory Acidosis
Under-elimination of hydrogen ions
Respiratory depression:
Anesthetics
Drugs (especially opioids)
Electrolyte imbalance
Inadequate chest expansion:
Muscle weakness
Airway obstruction
Alveolar-capillary block
Acid-Base Assessment
TEST
ARTERIAL
SIGNIFICANCE OF ABNORMAL FINDINGS
pH
7.35-7.45
Increased: Metabolic alkalosis, loss of gastric fluids, decreased potassium intake,
diuretic therapy, fever, salicylate toxicity, respiratory alkalosis, hyperventilation
Decreased: Metabolic or respiratory acidosis, ketosis, renal failure, starvation,
diarrhea, hyperthyroidism
TEST
ARTERIAL
SIGNIFICANCE OF ABNORMAL FINDINGS
PaO2
80-100 mm Hg
Increased: Increased ventilation, oxygen therapy, exercise
Decreased: Respiratory depression, high altitude, carbon monoxide poisoning,
decreased cardiac output, hypoxia
PaCO2
35-45 mm Hg
Increased: Respiratory acidosis, emphysema, pneumonia, cardiac failure, respiratory
depression
Decreased: Respiratory alkalosis, excessive ventilation, diarrhea
Bicarbonate
21-28 mEq/L
Increased: Metabolic alkalosis, bicarbonate therapy
Decreased: Metabolic acidosis, diarrhea, pancreatitis
Chapter 22: Care of Patients with Cancer
Tumor Lysis Syndrome (Oncological Emergency)
S/S: early: lethargy, N/V, anorexia, flank pain, muscle weakness, cramps, seizures, edema, altered mental
status; late: hyperkalemia, hyperuricemia, hyperphosphatemia, cardiac dysfunction
Treatment: hydration (3000-5000ml per day) (isotonic solution, sodium bicarbonate) to dilute the
concentration of the blood electrolytes, monitor daily weights and electrolytes, diuretics, kayexalate in
extreme cases, may need dialysis
SIADH (Oncological Emergency)
S/S: hyponatremia, extreme muscle weakness, muscle cramps, loss of appetite, fatigue, weight gain,
personality changes, decreased urine output, and increased osmolarity (treatment effective: increased
urine output, decreased osmolarity)
Treatment: focuses on treating the condition and cause, hypertonic solution (2% or 5% NS), restrict fluid,
increase sodium intake, immediate radiation/chemotherapy may cause enough tumor regression that
ADH production returns to normal
Chemotherapy
MOA: chemical agents that are used to kill cancer cells, interfere with cell division and regulation, are
useful in treating metastatic/rapidly dividing cancers (palliative nurse), can be used independently or
with other therapies
Complications: extravasation (drug leaks into surrounding tissue), vesicants (chemicals that damage
tissue on direct contact)
S/S: temporary or permanent damage to normal tissues, chemo-induced N/V, alopecia, mucositis,
stomatitis, cognitive changes, psychosocial issues, chemo-induced peripheral neuropathy, anemia,
thrombocytopenia, infection (bone marrow suppression and ), bladder toxicity, anxiety, neutropenia low
activity level (tolerable activity)

Patient Teaching: hand hygiene, staying at home as much as possible, personal hygiene, mouth care, PPE for
oral/home chemotherapy (no direct skin contact with an agent)
Radiation
Side Effects: acute or long-term site-specific skin changes (radiation dermatitis: redness and rash),
alopecia, altered taste, loss of appetite (eat 1 hour before therapy, liquids between meals, bland carbs
like cereal or crackers, avoid high-fat, cold/room temp. foods, sit up for 1 hour following), fatigue,
xerostomia (dry mouth), photosensitivity, bone marrow suppression, tissue fibrosis, and scarring
Patient Teaching: skin care (pat dry, no washcloths), do not remove temporary ink markings, wash skin
with mild soap and water/avoid scrubbing, avoid sun exposure, avoid alcohol-containing/aluminum-
containing products, frequent/gentle mouth care, swabs (no toothbrushes), use saliva substitutes,
regular dental visits, speech therapy, exercise, ensure good night sleep
Surgical Treatment
Complications: reduced function with organ loss, depression, altered appearance (scarring,
disfigurement), reduced activity level, cancer remains
Patient Teaching: encourage TCDB (turn, cough, deep breathing, spirometry), nutritional support
(radiation on the throat can cause speech/swallowing issues), early mobility, pain management, infection
prevention, psychosocial support, rehabilitation (PT, OT)
Infection Prevention: Low WBC Count
o Avoid crowds and other large gatherings of people who might be ill.
o Do not share personal toiletries such as toothbrushes, toothpaste, washcloths, or deodorant
sticks with others.
o If possible, bathe daily with antimicrobial soap. If total bathing is not possible, wash the
armpits, groin, genitals, and anal area twice a day with antimicrobial soap.
o Keep your toothbrush dry.
o Wash your hands thoroughly with an antimicrobial soap before you eat and drink, after touching
a pet, after shaking hands with anyone, as soon as you come home from any outing, and after
using the toilet.
o Follow the cancer center's instructions for eating fresh salads; raw fruits and vegetables; meat,
fish, and eggs; and pepper and paprika.
o Wash dishes between use with hot, sudsy water or use a dishwasher.
o Do not drink water, milk, juice, or other cold liquids that have been standing at room
temperature for longer than an hour.
o Do not reuse cups and glasses without washing them.
o Do not change pet litter boxes.
o Take your temperature at least once a day and whenever you do not feel well.
o Report any of these indications of infection to your oncologist immediately:
o Temperature greater than 100° F (37.8° C)
o A persistent cough (with or without sputum)
o Pus or foul-smelling drainage from any open skin area or normal body opening
o Presence of a boil or abscess
o Urine that is cloudy or foul-smelling or that causes burning on urination

o Take all prescribed drugs.
o Wear clean disposable gloves underneath gardening gloves when working in the garden or with
houseplants.
o Wear a condom when having sex. If you are a woman having sex with a male partner, ensure
that he wears a condom.
Chapter 53: Care of Patients with Oral Cavity Problems
Stomatitis
Patient Teaching (Diet): encourage frequent oral hygiene (rinse out mouth every 2 hours), avoid alcohol-
containing products, select soft/bland/nonacidic foods, avoid spicy/hard/salty/acidic foods, cool/cold
liquids (soothing), eat foods high in protein and vitamin C (promotes healing)
Oral Cancer
Risk Factors: increasing age (older than 40), tobacco use (cessation), alcohol use (avoid), HPV, poor oral
hygiene, periodontal disease, poor nutrition, occupation (textile workers, plumbers, metal workers, coal
miners), excessive sun exposure
Chapter 54: Care of Patients with Esophageal Problems
Hiatal Hernia
Etiology: protrusion of stomach through esophageal hiatus of the diaphragm into the chest; rolling
(obesity; reflux not present but volvulus/obstruction/strangulation high), sliding (structural defect,
anemia, most common)
Risk Factors: aging (weakening of diaphragm), smoking, obesity/straining
S/S: sliding (heartburn, regurgitation/reflux, chest pain, dysphagia, belching: worsens after a meal
or when the patient is supine), rolling (feeling of fullness/breathlessness after eating, feeling of
suffocation, chest pain that mimics angina, laying down worsens)
GERD
Patient Teaching: limit/eliminate foods that decrease pressure and cause irritation (i.e.: peppermint,
chocolate, alcohol, fatty foods, caffeine, carbonated beverages restrict spicy and acidic foods ),
(tomatoes, OJ), eat 4-6 small meals per day rather than 3 large ones, avoid eating at least 3 hours
before bedtime, eat slowly/chew thoroughly, medication adherence (PPIs: omeprazole), weight loss,
sit upright for 1 hour after eating, avoid NSAIDs
Chapter 55: Care of Patients with Stomach Disorders
Peritonitis: complication post abdominal surgery (high fever, rigid pain, tachycardia)
S/S: abdomen is tender, rigid, and board-like; abdominal pain and distention, N/V, anorexia, diminishing
bowel sounds, inability to pass flatus/feces (obstipation), high fever, tachycardia, dehydration, decreased
urine output, hiccups, rebound tenderness, possible compromise in respiratory status

Diagnostics (including labs): high WBC count (20,000 or above) and neutrophil count, blood culture
studies, fluid and electrolyte balance, renal status, O2 sat, ABGs, abdominal x-ray, ultrasound
PUD (H. pylori and NSAIDs)
Diagnostics: epigastric tenderness (between umbilicus and xiphoid process), dyspepsia, abdominal
pressure or fullness, urea breath test, stool antigen test, decreased H & H, chest and abdominal x-ray,
EGD (major test) endoscopy
Patient Teaching: medication adherence (drug regimen consists of a PPI and 2 antibiotics), avoiding
NSAIDs (use Tylenol/acetaminophen/analgesic), avoiding spicy/acidic foods, sitting upright after eating,
stress reduction
Duodenal Ulcers (type of peptic ulcer)
S/S: N/V, dyspepsia (indigestion), abdominal pressure/fullness, abdominal pain (RLQ) exacerbated by
food/NSAIDs/corticosteroids, epigastric tenderness (rigid, board-like abdomen with rebound
tenderness and pain), the pain usually occurs 90 mins.-3hrs. after eating, weight loss
Gastritis
Causes: H. pylori, long-term NSAID use, alcohol/coffee/caffeine/corticosteroid use, radiation therapy,
smoking, autoimmune disorders
Dumping Syndrome
Patient Teaching: eat high-protein, high-fat, low-to-moderate carbs, low roughage, no
milk/sweets/sugars, eliminate liquids with meals, eat small meals
Gastric Cancer
S/S: indigestion and abdominal discomfort (most common), , epigastric/back feeling of fullness
retrosternal pain; advanced: weight loss, N/V, weakness, fatigue, iron deficiency anemia, enlarged lymph
nodes, palpable epigastric masses, obstructive symptoms
Surgical Treatment: radiation and chemotherapy, surgical resection/partial or total gastrectomy
(preferred)
Complications: decreased NG tube patency (epigastric pain, feeling of fullness, hiccups, tachycardia,
hypotension) can result in acute gastric dilation, dumping syndrome (vertigo, tachycardia, syncope,
sweating, pallor, palpitations), alkaline reflux gastropathy (bile reflux gastropathy), delayed gastric
emptying, anemia, leukopenia, atrophic glossitis, aspiration from reflux, wound infection, bleeding,
respiratory complications, DVT
Patient Teaching: H. pylori and alcoholism increase risk, eat small/frequent meals, avoid drinking liquids
with meals, avoid foods that cause discomfort, eliminate caffeine/alcohol, smoking-cessation, lie flat
after eating for a short time, receive b12 injections as prescribed
Differences Between Gastric and Duodenal Ulcers
FEATURE
GASTRIC ULCER
DUODENAL ULCER
Age
Usually 50 yrs. or older
Usually 50 yrs. or older
Gender
Male/female ratio of 1.1:1
Male/female ratio of 1:1
General nourishment
Maybe malnourished
Usually well nourished
Stomach acid
production
Normal secretion or hyposecretion
Hypersecretion
Occurrence
Mucosa exposed to acid-pepsin
secretion
Mucosa exposed to acid-pepsin secretion
Clinical course
Healing and recurrence
Healing and recurrence
Pain
Occurs 30-60 min after a meal; at
night: rarely
Worsened by ingestion of food
Occurs 1.5-3 hrs. after a meal; at night: often awakens
patient between 1 and 2 AM
Relieved by ingestion of food
Hemorrhage
Hematemesis more common than
melena
Melena more common than hematemesis
Recurrence
Tends to heal and recurs often in the
same location
60% recur within 1 yr.; 90% recur within 2 yrs.
Surrounding mucosa
Atrophic gastritis
No gastritis
Early vs. Advanced Gastric Cancer
Chapter 56: Care of Patients with Non-inflammatory Intestinal Disorders
Colon Cancer: CEA (tumor marker)
S/S: common: rectal bleeding, anemia, change in stool consistency or shape changes in ; vomiting and
bowel elimination habits, fatigue, abdominal fullness, vague abdominal pain, unintentional weight loss
Risk Factors: 50 years of age or older, genetic predisposition, personal/family history, predisposing
conditions (familial adenomatous polyposis, Crohn’s disease, and ulcerative colitis)
Early Gastric Cancer
• Indigestion
• Abdominal discomfort was initially relieved with antacids
• Feeling of fullness
• Epigastric, back, or retrosternal pain
Advanced Gastric Cancer
• Nausea and vomiting
• Obstructive symptoms
• Iron deficiency anemia
• Palpable epigastric mass
• Enlarged lymph nodes
• Weakness and fatigue
• Progressive weight loss

Patient Teaching: recommend annual screening (fecal occult blood test) for patients over 50; post-op:
avoid lifting heavy objects or straining on defecation, avoid vigorous activity and driving for 4-6 weeks
(open surgical approach), consume foods high in fiber and protein, avoid red meats and eat veggies,
avoid foods that cause flatus (beans, eggs, carbonated beverages), odor (eggs, fish, garlic), and
obstruction (nuts, raw carrots, popcorn); proper colostomy care (wound care nurse), s/s of complications
Bowel Obstruction
S/S: obstipation, mid-abdominal pain/cramping, vomiting
Assessment: NG tube patency, placement, residual (COCA: color, odor, consistency, amount/volume),
output at least every 4 hours, dry mucous membranes (provide oral care), pain and abdominal
assessment (hyperactive bowel sounds=early; hypoactive bowel sounds=late)
Chapter 57: Care of Patients with Inflammatory Intestinal Disorders
Diverticulosis
Complications: diverticulitis can result in rupture of the diverticulum with peritonitis, pelvic abscess,
bowel obstruction, fistula, persistent fever or pain, or uncontrolled bleeding (bacteria in diverticula)
S/S: usually asymptomatic (found incidentally on routine colonoscopy), pain or bleeding may develop,
intermittent pain in LLQ, history of constipation, low-grade fever
Ulcerative Colitis
Complications: toxic megacolon, hemorrhage, dysplastic biopsy results, colon cancer
Patient Teaching: report pale blue/dark color of stoma, skin care, support groups, manifestations of GI
bleeding (black, tarry stool), rest to reduce intestinal activity/provide comfort/promote healing
Treatments: amino-salicylates, glucocorticoids, antidiarrheal drugs, immunomodulators; diet
modification (low-fiber/residue, high-protein, high-calorie), avoid dairy/alcohol/caffeine/raw
vegetables/carbonated beverages/pepper/nuts/corn/dried fruit/smoking, complementary therapies,
surgery, colon removal, ileostomy, NPO with TPN for severe cases, steroids=hyperglycemia
Side Effects: report N/V, anorexia, rash, headache with amino-salicylates; higher doses: hemolytic
anemia, hepatitis, male infertility, agranulocytosis
Crohn’s Disease
Complications: weight loss, anemia, severe malabsorption issues, , anal fissures, peritonitis, fistulas
bowel obstruction, nutrition, and fluid imbalances/deficiencies (malabsorption)
Appendicitis
Patient Teaching: RUQ pain (McBurney’s Point: between the anterior iliac crest and umbilicus),
remain in semi-fowler’s to contain drainage, lay on side with knees drawn up to relieve abdominal
tension
Inflammatory Bowel Disease (Ulcerative Colitis and Crohn’s Disease)
Treatment: glucocorticoid, loperamide (anti-diarrheal)
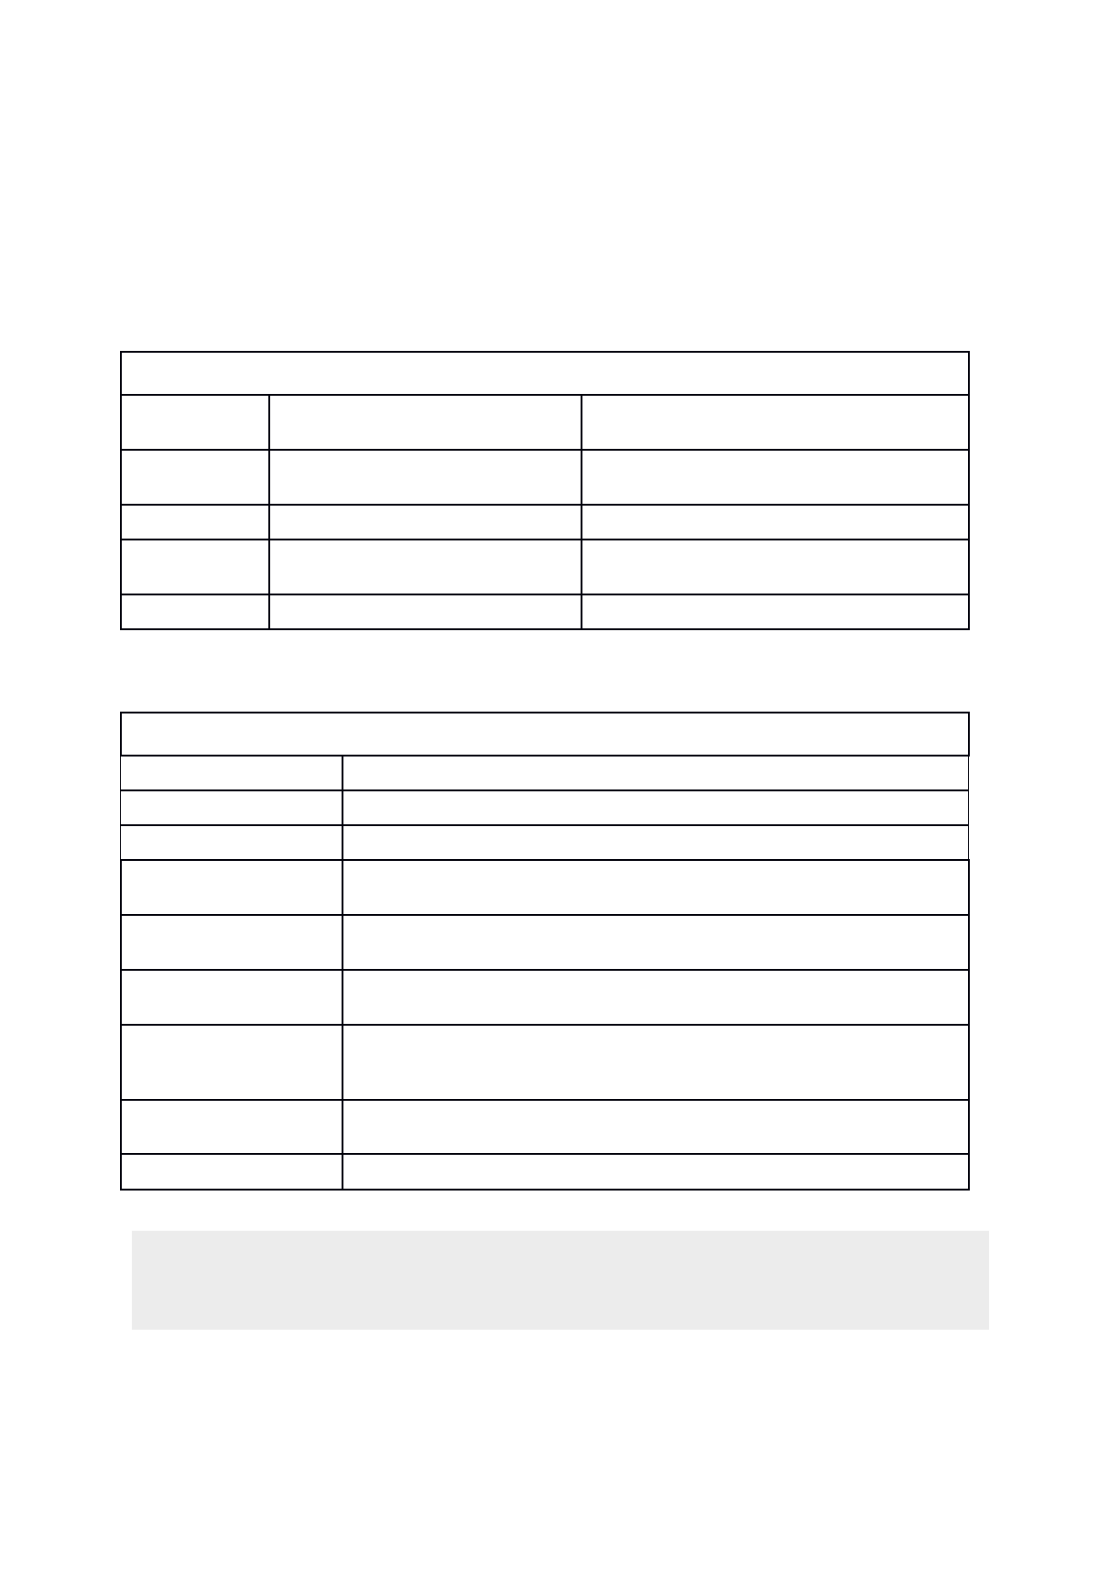
Differential Features of Ulcerative Colitis and Crohn’s Disease
FEATURE
ULCERATIVE COLITIS
CROHN'S DISEASE
Location
Begins in the rectum and proceeds
continuously toward the cecum
Most often in the terminal ileum, with patchy
involvement through all layers of the bowel
Peak incidence at
age
15-25 yrs. old and 55-65 yrs. old
15-40 yrs. old
Number of stools
10-20 liquid, bloody stools per day
5-6 soft, loose stools per day, not bloody
Complications
Hemorrhage
Nutritional deficiencies
Fistulas (common)
Nutritional deficiencies
Need for surgery
Infrequent
Frequent
Complications of Ulcerative Colitis and Crohn’s Disease
COMPLICATION
DESCRIPTION
Hemorrhage/perforation
Lower GI bleeding results from erosion of the bowel wall.
Abscess formation
Localized pockets of infection develop in the ulcerated bowel lining.
Toxic megacolon
Paralysis of the colon causes dilation and subsequent colonic ileus, possibly perforation.
Malabsorption
Essential nutrients cannot be absorbed through the diseased intestinal wall, causing
anemia and malnutrition (most common in Crohn's disease).
Nonmechanical bowel
obstruction
Obstruction results from toxic megacolon or cancer.
Fistulas
In Crohn's disease in which the inflammation is transmural, fistulas can occur anywhere
but usually track between the bowel and bladder, resulting in pyuria and fecaluria.
Colorectal cancer
Patients with ulcerative colitis with a history longer than 10 years have a high risk for
colorectal cancer. This complication accounts for about one-third of all deaths related
to ulcerative colitis.
Extraintestinal complications
Complications include arthritis, hepatic and biliary disease (especially cholelithiasis), oral
and skin lesions, and ocular disorders, such as iritis. The cause is unknown.
Osteoporosis
Osteoporosis occurs especially in patients with Crohn's disease.
Peritonitis S/S
• Rigid, board-like abdomen (classic)
• Abdominal pain (localized, poorly localized, or referred to as the shoulder or chest)
• Distended abdomen

Chapter 58: Care of Patients with Liver Problems
Cirrhosis
S/S: early: fatigue, significant change in weight, anorexia, vomiting, liver/abdominal tenderness; late:
jaundice, dry skin, rashes, petechiae, warm/bright red palms of hands, ecchymoses, spider angiomas,
ascites (abdominal fluid), peripheral dependent edema, vitamin deficiency
Diagnostics (including labs): bilirubin (itching), serum protein (decreased albumin), hematocrit,
electrolytes, liver enzymes, elevated AST and ALT, LDH, alkaline phosphatase, prolonged PT/INR,
elevated serum ammonia, WBCs, x-ray, ultrasound, MRI, biopsies
Esophageal Varices
Complications: bleeding varices (medical emergency), can result in shock from hypovolemia, loss of
consciousness; hematemesis or melena (black, tarry stool)
Hepatitis A
Risk Factors: adults over 40 years of age, pre-existing liver disease (hepatitis), recent travel
Transmission: fecal-oral route, contaminated food ( ) or water shellfish
Hepatitis B
Risk Factors: compromised immunity by disease/drug therapy, drug users, hepatitis carriers
Transmission: blood-body fluids, unprotected sex with an infected partner, sharing needles/syringes,
sharing razors/toothbrushes, accidental needlestick injuries, blood transfusions, hemodialysis, direct
contact with blood or open sores, transfer during birth
Hepatic Encephalopathy (the result of severe liver disease)
S/S: sleep and mood disturbances (labile), mental status changes, speech problems, altered LOC,
impaired thinking process, neuromuscular problems
Stages of Hepatic Encephalopathy
• Nausea, anorexia, vomiting
• Diminishing bowel sounds
• Inability to pass flatus or feces
• Rebound tenderness in the abdomen
• High fever
• Tachycardia
• Dehydration from high fever (poor skin turgor)
• Decreased urine output
• Hiccups
• Possible compromise in respiratory status
Stage I
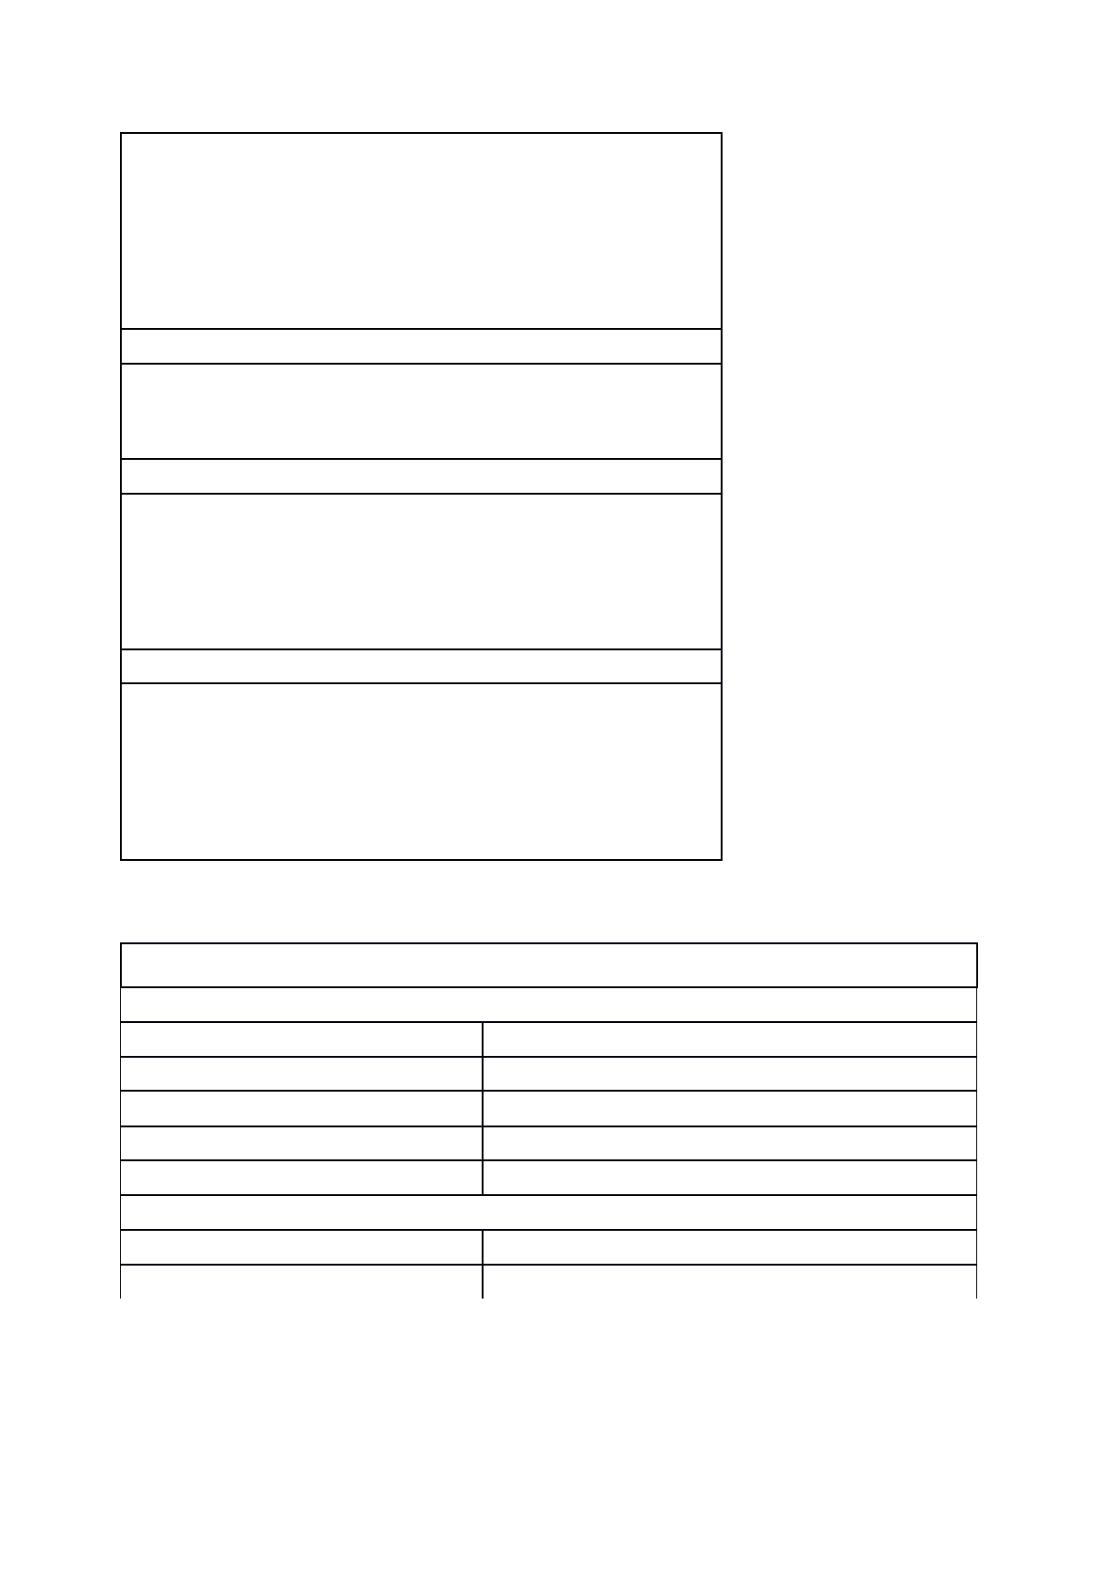
• Subtle manifestations that may not be recognized immediately
• Personality changes
• Behavior changes (agitation, belligerence)
• Emotional lability (euphoria, depression)
• Impaired thinking
• Inability to concentrate
• Fatigue, drowsiness
• Slurred or slowed speech
• Sleep pattern disturbances
Stage II
• Continuing mental changes
• Mental confusion
• Disorientation to time, place, or person
• Asterixis (hand flapping)
Stage III
• Progressive deterioration
• Marked mental confusion
• Stuporous, drowsy but arousable
• Abnormal electroencephalogram tracing
• Muscle twitching
• Hyperreflexia
• Asterixis (hand flapping)
Stage IV
• Unresponsiveness leads to death in most patients progressing to this stage
• Unarousable, obtunded
• Usually no response to painful stimulus
• No asterixis
• Positive Babinski's sign
• Muscle rigidity
• Fetor hepaticus (characteristic liver breath musty, sweet odor) —
• Seizures
Abnormal Laboratory Findings in Liver Disease
ABNORMAL FINDING SIGNIFICANCE
Serum Enzymes
Elevated serum aspartate aminotransferase (AST)
Hepatic cell destruction, hepatitis
Elevated serum alanine aminotransferase (ALT)
Hepatic cell destruction, hepatitis (most specific indicator)
Elevated lactate dehydrogenase (LDH)
Hepatic cell destruction
Elevated serum alkaline phosphatase
Obstructive jaundice, hepatic metastasis
Elevated gamma-glutamyl transpeptidase (GGT)
Biliary obstruction, cirrhosis
Bilirubin
Elevated serum total bilirubin
Hepatic cell disease
Elevated serum direct conjugated bilirubin
Hepatitis, liver metastasis
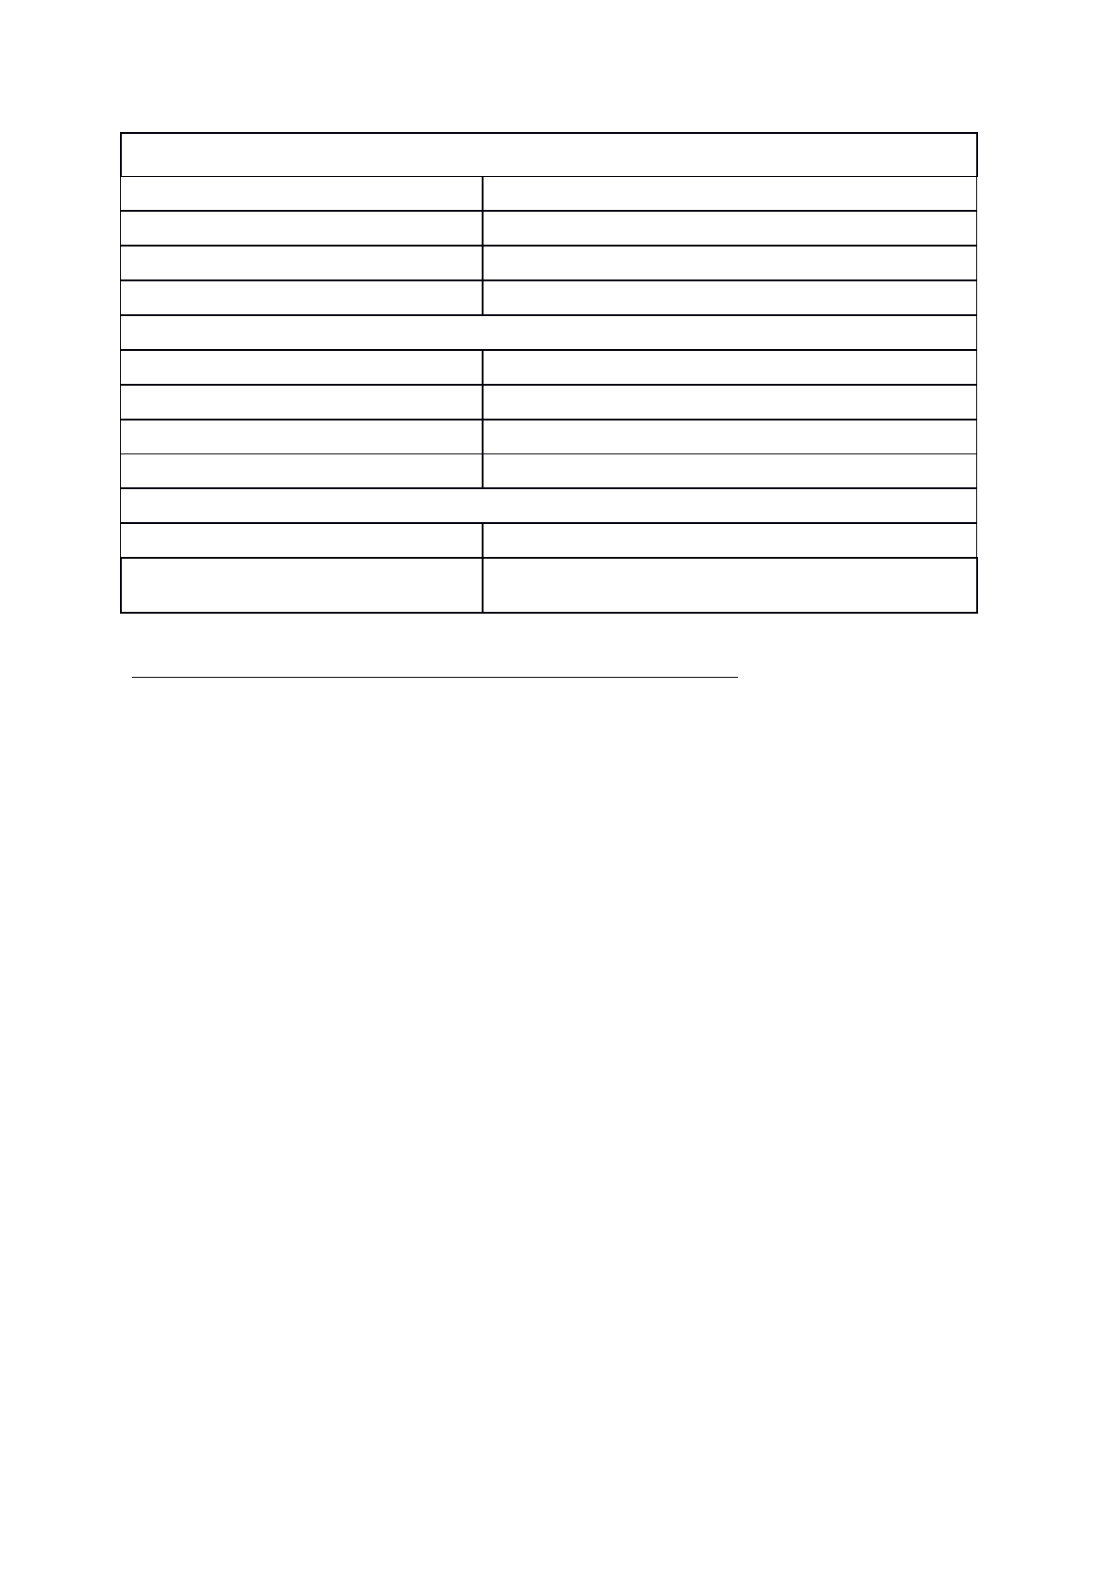
ABNORMAL FINDING SIGNIFICANCE
Elevated serum indirect unconjugated bilirubin
Cirrhosis
Elevated urine bilirubin
Hepatocellular obstruction, viral or toxic liver disease
Elevated urine urobilinogen
Hepatic dysfunction
Decreased fecal urobilinogen
Obstructive liver disease
Serum Proteins
Increased serum total protein
Acute liver disease
Decreased serum total protein
Chronic liver disease
Decreased serum albumin
Severe liver disease
Elevated serum globulin
Immune response to liver disease
Other Tests
Elevated serum ammonia
Advanced liver disease or portal-systemic encephalopathy (PSE)
Prolonged prothrombin time (PT) or international
normalized ratio (INR)
Hepatic cell damage and decreased synthesis of prothrombin
Chapter 59: Care of Patients with Problems of Biliary System and Pancreas
Pancreatitis
Causes: biliary tract disease (gallstones), cystic fibrosis, abdominal surgery, smoking, alcoholism,
genetics, renal failure, HIV infection, hypercalcemia, hyperlipidemia, hyperparathyroidism, pancreatic
obstruction, trauma, premature activation of pancreatic enzymes that destroy ductal tissue and
pancreatic cells (autodigestion and fibrosis result)
S/S: acute: severe pain in the mid-epigastric area or LUQ (intense, boring/piercing, continuous),
generalized jaundice, gray-blue discoloration of abdomen/flanks, weight loss; chronic: intense
abdominal pain and tenderness, ascites, LUQ mass, respiratory compromise, steatorrhea (clay-colored
stool), dark urine, diabetes mellitus/hyperglycemic (3 p’s)
Diagnostics (including labs): increased serum amylase/trypsin/lipase levels, elevated serum glucose,
decreased calcium and magnesium, WBCs, bilirubin, alkaline phosphatase, ALT, AST, abdominal
ultrasound, contrast-induced CT scan
Patient Teaching: NPO while in the acute phase, Whipple procedure or pancreatectomy (does not have to
be both), avoid alcohol and caffeine-containing foods (tea, chocolate, soda, coffee), report jaundice/clay-
colored stool/dark urine, same positioning as appendicitis
Cholecystitis
Patient Teaching: high-fiber, low-fat diet; small/frequent meals, lithotripsy (shock waves to breakdown
stones) and drug therapy for pain management
Teaching for Chronic Pancreatitis

• Avoid things that make your symptoms worse, such as drinking caffeinated beverages.
• Avoid alcohol ingestion; refer to a self-help group for assistance.
• Avoid nicotine.
• Eat bland, low-fat, high-protein, and moderate-carbohydrate meals; avoid gastric stimulants such as
spices.
• Eat small meals and snacks high in calories.
• Take the pancreatic enzymes that have been prescribed for you with meals.
• Rest frequently; restrict your activity to one floor until you regain your strength.
Causes of Diagnostic Laboratory Abnormalities in Acute Pancreatitis
ABNORMAL FINDING CAUSE
Cardinal Diagnostic Tests
Increased serum amylase
Pancreatic cell injury
Elevated serum lipase
Pancreatic cell injury
Elevated serum trypsin
Pancreatic cell injury
Elevated serum elastase
Pancreatic cell injury
Other Diagnostic Tests
Elevated serum glucose
Pancreatic cell injury, resulting in the impaired carbohydrate
metabolism; decreased insulin release
Decreased serum calcium and magnesium
Fatty acids combined with calcium; are seen in fat necrosis
Elevated bilirubin
Hepatobiliary obstructive process
Elevated alanine aminotransferase (ALT)
Hepatobiliary involvement
Elevated aspartate aminotransferase (AST)
Hepatobiliary involvement
Elevated leukocyte count
Inflammatory response
Chapter 62: Care of Patients with Pituitary and Adrenal Glands Problems
Addison’s (Adrenal Insufficiency)
Causes: inadequate secretion of cortisol/ACTH, dysfunction of the hypothalamic-pituitary control
mechanism, direct dysfunction of adrenal gland tissue, autoimmune disease, TB, AIDS, abdominal
radiation therapy, metastatic cancer, pituitary tumors, long-term corticosteroid drug therapy
S/S: anorexia, N/V, diarrhea, abdominal pain, weight loss (hypotension, hyponatremia, hypoglycemic,
hyperkalemia, hypercalcemia), anemia
Diagnostics (including labs): low serum cortisol, low fasting blood glucose, low sodium, elevated
potassium, increased BUN levels, ACTH stimulation test
Diabetes Insipidus

Treatment: Control of manifestations with drug therapy, desmopressin self-administration (oral, nasal),
vasopressin through ADH (posterior pituitary), hydration
Cushing’s Syndrome (Hypercortisolism, Hyperaldosteronism)
Causes: hypersecretion by the adrenal cortex caused by a pituitary adenoma (most common) or
glucocorticoid drug therapy (most at risk for infection)
S/S: fat pads on the neck, back, and shoulders; enlarged trunk with thin arms and legs, round face
(moon face), acne, HTN, hyperglycemia, loss of bone density, extreme muscle wasting, weight gain,
buffalo hump, thinning skin, emotional lability/mood swings (does not feel like self) (reversible)
Patient Teaching: infection prevention (hand hygiene, avoiding crowds, influenza vaccine), monitoring
weight (report 3lb. weight gain in 1 week), adherence, and side effects of hormone replacement
Cushing’s Disease (Hypercortisolism, Hyperaldosteronism)
S/S: same as a syndrome, to diagnosis disease from syndrome: , may also have cortisol in urine, most ACTH
commonly caused by pituitary adenoma
Acromegaly
S/S: overproduction of growth hormone in adults, enlargement of face/hands/feet, increased skeletal
thickness, skin hypertrophy, liver/heart enlargement, thickened lips, coarse facial features, barrel-shaped
chest, joint pain, hyperglycemia, sleep apnea
Adrenal Insufficiency S/S
Hypercortisolism (Cushing’s Disease/Syndrome) S/S
Neuromuscular Symptoms
• Muscle weakness
• Fatigue
• Joint/muscle pain
Gastrointestinal Symptoms
• Anorexia
• Nausea, vomiting
• Abdominal pain
• Constipation or diarrhea
• Weight loss
• Salt craving
Skin Symptoms
• Vitiligo
• Hyperpigmentation
Cardiovascular Symptoms
• Anemia
• Hypotension
• Hyponatremia
• Hyperkalemia
• Hypercalcemia

Chapter 63: Care of Patients with Thyroid and Parathyroid Problems (calcium most related to the thyroid)
Thyroid Storm
S/S: key symptoms: fever, tachycardia, systolic HTN; other symptoms: abdominal pain, N/V, diarrhea,
anxiety, tremors, restlessness, confusion, psychotic, seizures leading to coma (caused by pregnancy,
trauma, infection, stress, DKA)
Treatment: maintain airway, promote adequate ventilation and gas exchange, reduce fever, stabilize
hemodynamic status, do not give Synthroid/levothyroxine/thyroid meds
Hypoparathyroidism
Patient Teaching: consume foods high in calcium (grains/broccoli/kale)/low in phosphorus (no dairy,
peas, meat, eggs, legumes), medication adherence, interventions to reduce anxiety (stress therapy)
Hypothyroidism:
TSH is high, and T3 and T4 are low (myxedema coma, cold intolerance, weight gain, low HR)
Hyperthyroidism:
TSH is low in Grave’s, T3 and T4 are high (thyroid storm, heat intolerance, weight loss, exophthalmos,
goiter)
General Appearance
• Moon face
• Buffalo hump
• Truncal obesity
• Weight gain
Cardiovascular Symptoms
• Hypertension
• Frequent dependent edema
• Bruising
• Petechiae
Musculoskeletal Symptoms
• Muscle atrophy (most apparent in extremities)
• Osteoporosis (bone density loss)
• Pathologic fractures
• Decreased height with vertebral collapse
• Aseptic necrosis of the femur head
• Slow or poor healing of bone fractures
Skin Symptoms
• Thinning skin
• Striae and increased pigmentation
Immune System Symptoms
• Increased risk for infection
• Reduced immunity
• Decreased inflammatory responses
• Signs and symptoms of infection/inflammation possibly masked

Emergency Care of Patient During Thyroid Storm
Chapter 64: Care of Patients with Diabetes Mellitus
DMI (autoimmune)
Treatment: no cure, insulin therapy (rotate sites), nutrition interventions, pancreatic transplant
Complications: hypoglycemia, hyperglycemia, Somogyi phenomenon, cardiovascular disease, stroke,
DKA, HHS, reduced immunity, cognitive dysfunction, peripheral neuropathy (feet)
DMII (insulin resistant)
Treatment: hyperglycemic control (manage blood sugars), blood glucose monitoring, nutrition
interventions, exercise, drugs to lower blood glucose levels (insulin therapy only if blood glucose goals
cannot be met with the use of 2-3 different antidiabetic drugs: Metformin and Glucophage, must have
CT scan when on these meds, hold meds for 48 hours)
Complications: DKA, HHS, hypoglycemia (too much insulin or too little glucose), reduced immunity,
cardiovascular disease, cerebrovascular disease, diabetic retinopathy, diabetic nephropathy, sexual
dysfunction, cognitive dysfunction
Patient Teaching: low-calorie diet, increase physical exercise, weight loss, frequent eye exams
DKA/Hyperglycemia (low insulin and high blood glucose)
S/S: polyphagia (excess eating), polydipsia (excess thirst), polyuria (excess urination), fruity breath
odor, the risk for blood clots, ketone bodies, Kussmaul respirations, hemoconcentration, hypoxia,
sunken/soft eyeballs, lethargic
Treatment: fluid and electrolyte replacement (NS, hypotonic solution), acidosis management (sodium
bicarbonate), regular insulin therapy
Insulin
•
Maintain a patent airway and adequate ventilation.
•
Give oral antithyroid drugs as prescribed: methimazole (Tapazole), up to 60 mg daily;
propylthiouracil (PTU, Propyl-Thyracil), 300 to 900 mg daily.
•
Administer sodium iodide solution, 2 g IV daily as prescribed.
•
Give propranolol (Inderal, Detensol), 1 to 3 mg IV as prescribed. Give slowly over 3 minutes.
The patient should be connected to a cardiac monitor, and a central venous pressure catheter
should be in place.
•
Give glucocorticoids as prescribed: hydrocortisone, 100 to 500 mg IV daily; prednisone, 4 to
60 mg orally daily; or dexamethasone, 2 mg IM every 6 hours.
•
Monitor continually for cardiac dysrhythmias.
•
Monitor vital signs every 30 minutes.
•
Provide comfort measures, including a cooling blanket.
•
Give non-salicylate antipyretics as prescribed.
•
Correct dehydration with normal saline infusions.
•
Apply a cooling blanket or ice packs to reduce fever.

Short-Acting/Regular: 2-4 hour peak
Intermediate Acting/NPH: 8-hour peak
Hypoglycemia (high insulin and low glucose)
Treatment: glucose tablets/gel, fruit juice, carbs, calcium (if calcium is low, hypoglycemia occurs:
twitching and tetany), glucagon, and dextrose
Patient Teaching: do not delay meals for more than 30 minutes, do not take insulin if not planning to
eat, monitor glucose levels and adjust carb intake from readings, recommend a medical-alert bracelet,
consume 10-15g of carbs (recheck blood sugars in 15 minutes following), s/s (irritability, dizziness,
confusion, lack of coordination, diaphoresis), eat before exercise
Classification of Diabetes Mellitus
Type 1 Diabetes (T1DM)
• Beta-cell destruction leading to absolute insulin deficiency
• Autoimmune
• Idiopathic
Type 2 Diabetes (T2DM)
• Ranges from insulin resistance with relative insulin deficiency to secretory deficit with insulin resistance
Other Conditions Resulting in Hyperglycemia
• Genetic defects of beta-cell function
• Genetic defects in insulin action
• Pancreatic diseases (pancreatitis, trauma, cancer, cystic fibrosis, hemochromatosis)
• Endocrine problems (acromegaly, Cushing's disease, hyperthyroidism, aldosteronism)
• Drug- or chemical-induced hyperglycemia
• Infections: congenital rubella, cytomegalovirus, human immune deficiency virus
• Genetic syndromes associated with diabetes: Down syndrome, Klinefelter syndrome, Turner syndrome,
Huntington's disease, and others
Gestational Diabetes Mellitus (GDM)
• Glucose intolerance with onset or first recognition during pregnancy. (All pregnant women should be
screened.)
Differentiation of Type 1 and Type 2 Diabetes
Features
Type 1
Type 2
Former names
Juvenile-onset diabetes
Adult-onset diabetes
Ketosis-prone diabetes
Ketosis-resistant diabetes
Insulin-dependent diabetes mellitus (IDDM)
Non–insulin-dependent diabetes mellitus
(NIDDM)

Features Type 1 Type 2
Age at onset
Usually younger than 30 yrs. old
May occur at any age in adults
Symptoms
Abrupt onset, thirst, hunger, increased urine
output, weight loss
Frequently none; thirst, fatigue, blurred vision,
vascular or neural complications
Etiology
Viral infection, autoimmunity
Not known
Pathology
Pancreatic beta-cell destruction
Insulin resistance
Dysfunctional pancreatic beta cell
Nutritional status
Usually nonobese
60% to 80% obese
Insulin
All dependent on insulin
Required for 20% to 30%
Foot Care Instructions
• Inspect your feet daily, especially the area between the toes.
• Wash your feet daily with lukewarm water and soap. Dry thoroughly.
• Apply moisturizing cream to your feet after bathing. Do not apply to the area between your toes.
• Change into clean cotton socks every day.
• Do not wear the same pair of shoes 2 days in a row and wear only shoes made of breathable materials,
such as leather or cloth.
• Check your shoes for foreign objects (nails, pebbles) before putting them on. Check inside the shoes for
cracks or tears in the lining.
• Purchase shoes that have plenty of room for your toes. Buy shoes later in the day, when feet are
normally larger. Break in new shoes gradually.
• Wear socks to keep your feet warm.
• Trim your nails straight across with a nail clipper. Smooth the nails with an emery board.
• See your physician or nurse immediately if you have blisters, sores, or infections. Protect the area with
a dry, sterile dressing. Do not use adhesive tape to secure the dressing to the skin.
• Do not treat blisters, sores, or infections with home remedies.
• Do not smoke.
• Do not step into the bathtub without checking the temperature of the water with your wrist or
thermometer. The optimal temperature is 95° F (35° C). The maximum temperature is 110° F
(43° C).
• Do not use very hot or cold water. Never use hot water bottles, heating pads, or portable heaters to
warm your feet.
• Do not treat corns, blisters, bunions, calluses, or ingrown toenails yourself.
• Do not go barefooted.
• Do not wear sandals with open toes or straps between the toes.
• Do not cross your legs or wear garters or tight stockings that constrict blood flow.
• Do not soak your feet.
Difference Between DKA and HHS
DIABETIC KETOACIDOSIS (DKA)
HYPERGLYCEMIC-HYPEROSMOLAR STATE (HHS)
Onset
Sudden
Gradual
Precipitating
factors
Infection
Infection
Other stressors
Other stressors

DIABETIC KETOACIDOSIS (DKA)
HYPERGLYCEMIC-HYPEROSMOLAR STATE (HHS)
Inadequate insulin dose
Poor fluid intake
Symptoms
Ketosis: Kussmaul respiration, “rotting fruit” breath,
nausea, abdominal pain
Altered central nervous system function with
neurologic symptoms
Dehydration or electrolyte loss: polyuria, polydipsia,
weight loss, dry skin, sunken eyes, soft
eyeballs, lethargy, coma
Dehydration or electrolyte loss: same as for DKA
Laboratory Findings
Serum glucose
>300 mg/dL (16.7 mmol/L)
>600 mg/dL (33.3 mmol/L)
Osmolarity/
Osmolality
Variable
>320 mOsm/L (mOsm/kg)
Serum ketones
Positive at 1: 2 dilutions
Negative
Serum pH
<7.35
>7.4
Serum
<15 mEq/L (mmol/L)
>20 mEq/L (mmol/L)
Serum Na
+
Low, normal, or high
Normal or low
BUN
>30 mg/dL (10 mmol/L); elevated because of
dehydration
Elevated
Creatinine
>1.5 mg/dL (60 mcmol/L); elevated because of
dehydration
Elevated
Urine ketones
Positive
Negative

