



1
Chapter 1: Introduction
Cancer Immunotherapy, the 2013 “Breakthrough of the Year” leverages the patient’s immune
system to seek out and specifically kill the cancer cells[1]. The origin of the idea to harness
the potential of the immune system in cancer treatment dates back to the 19th century when
William Coley injected his cancer patient with heat inactivated bacteria and observed tumor
regression as a result of an activated immune system[2]. The intellectual momentum that
began with Coley’s observation took several decades of scientific research to finally place
immunotherapy at the centerstage of cancer treatment in the 21st century[3,4]. The concerted
efforts of basic science researchers and clinicians over the past century finally led to The Food
and Drug Administration (FDA) approval of Ipilimumab in 2011, a monoclonal antibody for the
treatment of unresectable or metastatic melanoma and firmly established Immunotherapy as
the fifth pillar of cancer treatment[5,6].
Allison and his colleagues’ curiosity to study the fundamental mechanisms of T cell regulation
led to their discovery of CTLA-4, the molecular target of Ipilimumab on T cells[7,8]. In parallel,
Honjo and his colleagues serendipitously discovered PD-1 which like CTLA-4 inhibited T cell
effector function albeit via a different mechanism of action[9,10]. With the FDA approval of
Pembrolizumab in 2015, a monoclonal antibody against PD-1, a distinct class of
Immunotherapy for cancer called the Immune Checkpoint Inhibitors (ICI) was formed[11,12].
In the past decade the FDA approved seven antibodies targeting the PD-1 co-receptor and
its ligand PD-L1 for the treatment of more than 85 oncology indications[13]. The incremental
understanding provided by studying the underlying fundamental mechanisms constantly
informed novel discoveries and treatments in the clinic. Currently more than 2000 clinical trials
are evaluating the efficacy of anti-PD1/PDL1 mAbs in combination with other treatments for
cancer. While ICI revolutionized cancer treatment and demonstrated that long-term remission

2
even with discontinued treatment is possible in a minority of patients, those who are refractory
to or relapse after treatment continue to remain in the majority[14,15].
The clinical applicability of ICI and other combination therapies can be expanded only through
a comprehensive understanding of the molecular mechanisms that dictate the dynamic
interaction between the tumor and the immune system. The clinical development of novel
treatment strategies relies on rigorous basic science research and its subsequent clinical
translation.
In Chapter 1, I will present background information necessary to understand and appreciate
the significance of my PhD research work. I will explain the background information in the
following order and present the objective of this dissertation:
1) Hide and seek: Cancer Vs Immune System
2) Immune checkpoint protein: PD-1 co-receptor
3) The role of PD-1 in different contexts of immune response
4) The therapeutic landscape of PD-1/PD-L1/PD-L2 signaling axis

3
1.1 Hide and seek: Cancer Vs Immune System
The field of oncology until the early 20th century relied on radiotherapy and chemotherapeutic
approaches for advancing cancer treatment[16]. In 1957 Burnet and Thomas postulated that
cancer cells accumulate “non-self” antigens that can stimulate the immune system and result
in regression of the tumor[17]. Their hypothesis received its long overdue validation in 2001
when Schreiber and colleagues showed that immune deficient mice, specifically lacking IFN-
ʏ and lymphocytes were more susceptible to carcinogen induced sarcoma than immune-
competent mice[18]. Schreiber refined the concept of cancer immunosurveillance and
proposed the term ‘cancer immunoediting’ and emphasized the ability of cancer cells to adapt
and outgrow the survival pressures exerted by the immune system and escape immune
detection[19,20]. Cancer immunoediting progresses through three distinct phases of
elimination, equilibrium, and escape[21–23].
The elimination phase retains the concept of immunosurveillance wherein immune cells patrol
the body to restrict the growth of malignant cells through inflammation. The immune system
specifically recognizes tumor-specific antigens (TSA) on transformed cells and eliminates
them through a diverse range of immune effector cells and molecules[24]. Seminal studies
like the discovery of interferons by Isaacs and Lindenmann in 1957, the role of T cells in
adaptive immunity by Miller in 1967 and the discovery of dendritic cells by Steinman and Cohn
in 1973 laid the foundation to infer the inherent anti-tumor potential of the immune system[25–
29]. The elimination phase ensures that developing tumors are destroyed and are clinically
undetectable in the body. The innate and adaptive immune systems work in harmony to carry
out immunosurveillance and protect the host from the development of any malignancies.
Since the end point of the elimination phase is the absence of cancer, experimental models
accurately representing this phase are limited[30].

4
Tumor cells that survive the elimination phase enter into a dynamic equilibrium with the
immune system during which the immune system is able to only contain the growth of the
tumor and not fully eradicate the tumor. During this phase of tumor dormancy, the transformed
cells continue to accumulate mutations as a result of the cancer cell’s intrinsic genetic
instability and gives rise to new variants that provide increased protection from any anti-tumor
immune response[31].
The Darwinian selection of variants leads to the escape phase of cancer immunoediting
wherein tumor cells grow and metastasize uncontrollably by avoiding recognition and
elimination by the immune system[32]. Adaptations in tumor cell intrinsic mechanisms like
mutational landscape, metabolic fitness, etc. together with tumor cell extrinsic factors like the
tumor microenvironment (TME), host-related factors like microbiota drive the immune escape
of cancer[32–40]. The function of T cells to specifically recognize tumor associated antigens
in the context of MHC molecules to carry out direct cytotoxic reactions against neoplastic cells
and form immunological memory placed them in the spotlight to dismantle the escape phase
and promote anti-tumor immunity[41]. While immune cells like T cells and NK cells are
emblematic of the cancer-killing potential of the immune system, an effective anti-tumor
response requires a series of stepwise events explained in the Cancer Immunity Cycle that
precedes the final blow served by T cells and NK cells[42].
The TME orchestrates a complex network of interactions that creates roadblocks at various
stages of the cancer immunity cycle to prevent an onslaught by the immune system. TME
constitutes molecular players like endothelial cells, immune cells, extracellular matrix, and
vasculature that create a favorable neighborhood for malignant cells to grow and flourish into
aggressive cancers[43–45]. The hallmark features of a pro-tumor TME are a hypoxic niche,
immunosuppressive stromal cells, increased lactate and ROS metabolism, expression of
immune checkpoint proteins and the more recently appreciated a stiff mechanical scaffold and

5
an innervated niche that supports metastasis[46,47]. Therapeutically targeting the TME is like
a game of Jenga but with the goal of destabilizing the structure. A single block will not weaken
the structure, however a strategic removal of a combination of blocks will let the tower fall. In
the last several decades cancer immunologists are focused on attacking the tumor from
multiple fronts to achieve durable clinical responses[48].
Allison and Honjo’s seminal discovery that blockade of immune checkpoint proteins can
mobilize anti-immune response was the advent of modern immunotherapy against cancer.
For the first time immune checkpoint inhibitors made long term remission a possibility for some
cancer patients and provided a new vision for cancer management. In spite of the hope that
ICI gave rise to, it is not the ultimate answer for cancer treatment. It is important to
acknowledge that innovation and improvement of novel therapeutics against immune
checkpoint proteins can be achieved only through a comprehensive understanding of the
associated immunobiology, which in turn will aid scientists and clinicians to anticipate possible
evasion mechanisms of the tumor or be aware of any potential off-target clinical effects.

6
1.2 Immune checkpoint protein: PD-1 co-receptor
Immune checkpoint proteins are gatekeepers that maintain self-tolerance and temper the
intensity of immune responses in normal human physiology to prevent any collateral
damage[49,50]. A number of immune checkpoint proteins have been discovered and
investigated for therapeutic benefit against cancer, for example, PD-1, CTLA-4, PD-L1, PD-
L2, TIGIT, LAG3, TIM3, ILT2, B7H3, BTLA, KIR, NKG2A and CD96. FDA-approved inhibitors
against PD-1, CTLA-4 and PD-L1 revolutionized the landscape of cancer immunotherapy and
other proteins are being actively investigated for the next generation of immune checkpoint
blockade[51,52]. A monoclonal antibody against CTLA-4 (Ipilimumab) was the first immune
checkpoint inhibitor that received FDA approval in 2011 for unresectable, late-stage
melanoma. While Ipilimumab and Tremelimumab remain as the only FDA-approved
monoclonal antibody (mAb) against CTLA-4, our arsenal against PD-1 is expanding with 4
FDA-approved mAbs (Nivolumab, Pembrolizumab, Cemiplimab and Dostarlimab)[6,53].
Many attribute the severity of side-effects associated with CTLA-4 blockade and it’s restricted
mode of action in lymphoid tissues as the reason behind the preference for PD-1
blockade[54,55].
Programmed cell death-1 (PD-1 or CD279) is a transmembrane protein and a member of the
CD28/B7 superfamily[56]. It is mainly expressed on activated T cells and binds to two known
ligands, PD-L1 (CD274) or PD-L2 (CD273) to inhibit proliferation and effector functions of T
cells. PD-1 is a type 1 transmembrane glycoprotein with a single extracellular IgV domain, a
hydrophobic transmembrane domain, and a cytoplasmic tail with two pivotal signaling
domains, namely, immunoreceptor tyrosine-based inhibitory motif (ITIM) and immunoreceptor
tyrosine-based inhibitory motif (ITSM)[57]. Initially thought to be expressed only on activated
T cells, PD-1 expression is now appreciated in other cells such as Natural Killer (NK) cells,
Dendritic cells (DCs), Macrophages, Tumor cells, B cells, Myeloid derived suppressor cells

7
(MDSCs), and Tregs[58,59]. It is generally inferred from previous studies that PD-1 on effector
immune cells inhibit their effector function whereas PD-1 on suppressive immune cells like
Tregs remains controversial and warrants future investigation. This further emphasizes the
complexity of immune therapy and the need to continue investigating the immunobiology of
therapeutic targets for yet to be discovered biological impacts.
The extracellular domain of PD-1 contains a β sheet face that engages the ligands. Murine
PD-L1 and PD-L2 have comparable binding affinities to PD-1 but human PD-L2 exhibits a 2-
6 fold higher affinity to human PD-1 than PD-L1[60]. Structural studies of human PD-1/ PD-
L1 and PD-1/PD-L2 complexes revealed that distinct amino acid residues in the extracellular
domain of PD-1 are engaged by PD-L1 and PD-L2 resulting in significant differences in the
interfaces formed[61]. Whether these differences result in major conformational
rearrangement of the transmembrane protein is yet to be demonstrated. While it is classically
accepted that PD-1 on T cells binds to PD-L1 on antigen presenting cells (APCs), recent
reports support a possible cis interaction between PD-1 and PD-L1 as well[62]. Besides
interacting with PD-1, PD-L1 is also reported to interact with CD80, a co-stimulatory ligand
that engages the CD28 receptor on T cells[63]. PD-L2 does not bind to CD80 and is reported
to bind a second receptor called Repulsive guidance molecule-b (RGMb) in mouse models.
CD80 binds to PD-L1 when co-expressed on the same cell (cis-CD80/PD-L1) and disrupts
the PD-1/PD-L1 complex formation while retaining the CD28/CD80 interaction. The cis-
CD80/PD-L1 complex recruits PD-L1 away from PD-1 and CD80 from CTLA-4 mediated
trans-endocytosis resulting in a net co-stimulatory effect on T cells[64]. The role of PD-L2
remains unresolved with conflicting evidence suggesting both co-stimulatory as well as co-
inhibitory functions. The non-linear interactions between immune checkpoint proteins add
several layers of complexity that need to be considered for designing therapeutic
interventions.

8
Mutational studies show that PD-1/PD-L1 inhibitory function depends on the Lck mediated
ITSM phosphotyrosine that preferentially recruits SHP-2 phosphatase to downregulate T cell
activation[65–67]. Single cell imaging experiments elucidated a molecular mechanism of PD-
1 inhibition wherein PD-1/PD-L clustered with TCR to form a microcluster that induces the
dephosphorylation of the membrane proximal TCR signaling molecules[68]. The role of ITIM
in PD-1 mediated signaling is explained by contradicting models of protein interaction. In one
model it is postulated that ITSM strongly binds to the C-SH2 domain of SHP-2 and recruits
the phosphatase proximal to the membrane, while the ITIM binds to the N-SH2 domain and
activates the phosphatase. In a different model it is shown that the N-SH2 and C-SH2 domains
of SHP-2 could bridge two phosphorylated ITSM regions on two PD-1 tails to form a PD-1:
PD-1 dimer at the plasma membrane[69]. While it is mostly accepted that SHP-2 is the only
immediate partner of PD-1, but a recent report showed mice with SHP-2 deleted T cells
capable of PD-1 mediated inhibition indicative of a possible SHP-2 independent downstream
signaling of PD-1[70]. PD-1 ligation ultimately results in the dephosphorylation of the TCR-
CD3 and CD28 signaling axis leading to the inhibition of PI3K/Akt, MAPK and mTOR
pathways in T cells[71]. PD-1 is also able to reprogram the metabolic state of T cells by
favoring fatty acids in β-oxidation over glycolysis and by decreasing the threshold of TGF-β
mediated signaling[72].

9
1.3 Diverse roles of the PD-1 signaling axis
Immune checkpoint proteins regulate T cell responses through ligand-receptor interactions
during different contexts of inflammation and T cell differentiation. In addition to regulating the
effector functions of T cells, PD-1 can also regulate T cell memory responses as well. At the
time of first encounter with an antigen, the strength of the TCR signal will dictate the balance
between effector responses vs memory responses[73,74]. The precise role of PD-1 in
influencing immunological memory is dependent on variables such as type of immune
pressure, tissue context, stage of T cell response and TCR signal strength.
PD-1 was first implicated in the regulation of T-cell tolerance and autoimmunity when the
phenotype of PD-1-/- mice was characterized by late onset of lupus-like disease and mild
glomerulonephritis in C57BL/6 mice[75]. The inhibitory signal delivered by the PD-1/PD-
L1/PD-L2 axis can regulate both central and peripheral T-cell tolerance in normal human
physiology[76].For example, the PD-1/PD-L1 complex restricts positive selection in the CD4-
CD8- (DN) to CD4+CD8+ (DP) stage of T cell development in the thymus. In the periphery,
PD-1 inhibits the initial phase of activation and expansion of self-reactive T cells and prevents
any organ injury by self-reactive T cells. PD-1 is also known to enforce a cell intrinsic
mechanism of restraint on Tregs, such that PD-1 deficient Tregs exhibit enhances
immunosuppressive function[77]. PD-1 and PD-L1 were implicated in the pathogenesis of
Type 1 diabetes (T1D) in mouse models. Similarly, the PD-1 signaling axis was studied in the
context of Multiple Sclerosis, Inflammatory bowel disease and rheumatoid arthritis[76]. These
studies focused only on the PD-1/PD-L1 interaction and extrapolated it to be true for PD-1/PD-
L2 binding as well. Only recently the specific role of the PD-1/PD-L2 axis in airway immune
tolerance was studied to show that PD-L2 promoted the maintenance of Foxp3+ pTregs by
supporting their metabolic activity and Foxp3 stability[78]. This observation is aligned with a

10
different study that showed a positive correlation between the severity of asthma and absence
of PD-L2[79].
During acute infections like malaria and chronic infections like HIV or Hepatitis B virus immune
checkpoint molecules are upregulated on T cells and restrict immune-mediated clearance of
the infection[80]. The severity of PD-1 mediated exhaustion in T cells is proportional to the
viral load that ultimately results in the elimination of antigen-specific T cells[81]. Recent studies
of malaria contributed to the contention around PD-L2 and showed that higher expression of
PD-L2 on blood DCs correlated with lower parasitemia[82]. The study postulated that PD-
1/PD-L2 complex outcompetes PD-1/PD-L2 interaction to protect T cells from PD-1/PD-L1
mediated exhaustion during malarial infection. During chronic HIV or HBV infection PD-1 is
overexpressed on CD4+ and CD8+ T cells and correlated with increased disease progression
and higher viral load. Immune checkpoint blockade in viral infections like HIV could have
beneficial outcomes like increased vaccine responsiveness or increased HIV-specific T cell
function to eliminate HIV-infected cells[83].
Maternal-fetal immunotolerance is a unique challenge faced by the immune system where the
mother’s immune system has to restraint immune responses against the semiallogenic fetus
while protecting the mother from other infections[84]. At the maternal-fetal interface high
expression of PD-1 is found on decidual T cells that reduce Th1 type of immune response at
the maternal-fetal interface during a healthy human pregnancy[85]. In mice, blockade of the
PD-1 pathway during pregnancy increased T cell infiltration and Th1 cytokine production in
the placenta resulting in decreased pup survival[86]. During gestation PD-ligands showed
different expression patterns, but the physiological relevance of the difference is still known.
PD-L1 is expressed on the villous synctiotrophoblast and extravillous cytotrophoblast while
PD-L2 is limited to villous cytotrophoblast[87,88]. An interesting study demonstrated that the
function of PD-L2 was modified during the evolutionary transition from marsupial to placental

11
mammals, emphasizing a possible unique role of PD-L2 in the placenta that is not shared with
PD-L1[89].
The PD-1 pathway is efficiently hijacked by the tumor to evade the immune system and
bolsters the clinical progression of the disease. PD-1+ tumor infiltrating lymphocytes (TILs)
observed in several human cancers are characterized by impaired effector cytokine
production, increased expression of multiple inhibitory receptors, altered metabolism and loss
of proliferating capacity[90]. PD-L2 is widely expressed across many types of cancers, in
tumor cells, endothelial cells as well as on immunosuppressive stromal cells. The expression
of PD-L2 in human cancers is only recently appreciated and was shown to be a better
predictor of progression-free survival with pembrolizumab in head and neck squamous cell
carcinoma than PD-L1 [91]. However, preclinical studies in murine models suggest that PD-
L2 promotes tumor immunity through a PD-1 independent mechanism[92]. In the last decade
several studies investigated the role of PD-1 on immune cells other than T cell as well as on
nonimmune cells[59,93–95]. The discovery of PD-1 on tumor cells and subsequent research
on it has led to the “tumor cell-intrinsic PD-1/L1 paradox”[96,97]. While PD-1 is a potential
oncogene in pancreatic, melanoma, and bladder cancer cells, but is reported to be a tumor
suppressor in non-small cell lung cancer and colon cancer cells. A previous study reported
the rapid disease progression of stage IV NSCLC in a 61-year old woman after treatment with
pembrolizumab[98–100]. The precise molecular mechanism underlying this paradox is
important to decipher since it will inform current and future clinical potential of PD-1 blockade.
This also emphasizes the non-canonical cis-PD-1/PD-L1 interaction that may be at play on
the surface of tumor cells expressing PD-1 and PD-L1[101]. Recently, it was reported that
PD-1 on dendritic cells (DCs) neutralized PD-L1 in cis to inhibit PD-1 signaling in T cells[102].
Additionally, it is also important to understand the role of PD-L2 during non-canonical
interactions of PD-1 since human cancers are now known to upregulate both the PD-ligands.

12
The field has come a long way from describing the PD-1 signaling axis as a simple on/off
switch that regulates T cell function to an intricate signaling repertoire characterized by a
gradient in the intensity of responses. Since PD-1 and its ligands are expressed on a wide
variety of cells, therefore current and future therapies should be cognizant of the functional
consequence of disrupting the PD-1/PD-L1/PD-L2 signaling axis on different cellular
compartments that may yield new potential targets for combinatorial therapies.
1.4 Therapeutic landscape of the PD-1/PD-L1/PD-L2 signaling axis
As of 2022, 4,897 active clinical trials are investigating anti-PD1/PDL1 mAbs as a single agent
or in combination with other therapies[103]. The majority of these clinical trials are evaluating
combination therapies affirming that the future of immunotherapy for cancer relies on
mechanism of action based synergies of drug therapies. FDA-approved mAbs against PD-
1/PD-L1 include Pembrolizumab, Nivolumab, Durvalumab, Atezolizumab, Avelumab,
Cemiplimab and Dostarlimb[6]. Pembrolizumab, is a human IgG4κ monoclonal antibody
against PD-1 that was first approved in 2014 in metastatic melanoma patients who were
refractory to CTLA-4 therapy and is investigated in the highest number of clinical trials in
comparison to other mAbs in the PD-1/PD-L1 arsenal. Since 2014, anti PD-1/PD-L1 mAbs
have been FDA-approved for several cancers with the latest one on February 9, 2023, for
dostarlimab in adult patients with mismatch repair deficient (dMMR) recurrent or advanced
endometrial cancer. Through these clinical trials the field of Immunotherapy aims to achieve
the holy grail of cancer treatment, that is, maximal tumor clearance with minimal treatment
associated toxicities. 10% of patients receiving anti-PD-1 antibodies have grade 3 immune
related adverse events (irAEs) that mostly occur within 6 months of treatment[104]. The most
common irAEs associated with PD-1 blockade include pneumonitis, hepatitis, colitis,
endocrinopathies and diarrhea[105–107]. A meta-analysis of 19 clinical trials studying anti-
PD-1/PD-L1 antibodies showed a higher incidence of pneumonitis in patients receiving anti-

13
PD-L1 antibodies. The comparatively lower incidence of anti-PD-L1 blockade may be due to
the preservation of PD-1/PD-L2 interaction that maintained immune homeostasis in
patients[108]. A recent study showed that PD-L1 antibodies like atezolizumab, avelumab and
durvalumab were superior to PD-1 antibodies like pembrolizumab and nivolumab to disrupt
the PD-1 signaling axis[109]. This was the first time therapeutic antibodies with similar
mechanisms of action were compared directly against each other. Even though both PD-1
and PD-L1 antibodies target the PD-1 signaling axis, the multi-directional interactions of
proteins in the B7/CD28 family results in unique clinical consequences of these
therapies[110].
While the current clinical landscape of PD-1/PD-L1 blockade reflects innovation and a
promising future for immunotherapy and cancer treatment, it also necessitates the need to
avoid duplicative development programs. Through the inception of Project Orbis, the FDA
Oncology Center of Excellence seeks to harmonize the various drug development programs
and achieve greater efficiency in patient care and treatment[111]. The unprecedented durable
responses of PD-1/PD-L1 blockade are a reality for only a small population of patients, while
the majority either do not respond to the therapy at all (primary resistance) or relapse after a
short period of response to immunotherapy (acquired resistance)[112]. Resistance to PD-
1/PD-L1 blockade can be driven by tumor cell intrinsic or tumor cell extrinsic factors[113].
Tumor cell intrinsic factors include mechanisms like altered antigen-presenting machinery,
expression of immunosuppressive ligands, mutations in interferon gamma signaling,
oncogenic signaling through the MAPK pathway, and upregulation of genes associated with
mesenchymal transformation[113–117]. Tumor cell extrinsic factors that support resistance to
immunotherapy include cells like Tregs, MDSCs, M2 macrophages and an
immunosuppressive metabolic microenvironment[118–120]. Alternate inhibitory immune
checkpoints like TIM-3, LAG-3, TIGIT and VISTA can compensate for the PD-1/PD-L1

14
blockade and result in unresponsive cancers to therapy[121]. Several cancers employ
immune suppression, immune exclusion, and immune ignorance to prevent anti-tumor
immune response[122]. The majority of modern immunotherapy is focused on combinatorial
approaches to strategically tear down the above mentioned resistance mechanisms of the
tumor. A clear understanding of the immunobiology underlying the therapeutic targets is
fundamental to designing combinatorial therapies with optimal synergies in the clinic.

15
1.5 Objective of the dissertation
The need for durable therapy against cancer encouraged the clinical translation of immune
checkpoint blockade and the subsequent accelerated clinical expansion to different cancer
types. The therapeutic efficacy of immune checkpoint proteins is built upon an incomplete
understanding of the mechanistic biology that dictates the crosstalk between these proteins.
The newly discovered cis interaction between PD-L1 and CD80 expands on the current model
of PD-1/PD-L1 and CTLA-4/CD80 signaling axis and presents a new perspective for
therapeutic intervention[64]. The paradoxical role of tumor-intrinsic PD-1 as an oncogene in
some cancers vs as a tumor suppressor in others was a recent discovery that may help refine
PD-1 blockade as a therapy in the clinic. Studies like this make it clear to the field that there
is still a lot unknown about the complex multi-directional interactions of PD-1 and its ligands.
Despite the concerted efforts between immunologists and clinicians to delineate the PD-1
signaling axis, our understanding will continue to remain incomplete until we appreciate the
role of PD-L2 in PD-1 mediated T cell inhibition. So far, PD-L2 is assumed to be a redundant
ligand of the PD-1 co-receptor on T cells based on preclinical mouse models that may not
accurately represent the role of PD-L2 in humans. Through this dissertation work we seek to
provide a deeper insight into the molecular relationship between PD-1, PD-L1 and PD-L2 and
to highlight the functional outcome of the differential interaction between PD-1, PD-L1 and
PD-L2. We hypothesize that PD-L2 is solely a co-inhibitory ligand in humans that
transduces an inhibitory signal via PD-1 that is distinct from PD-L1. We propose to (1)
define the function of PD-L2 in humans, (2) delineate the inhibitory signal mediated by PD-L2
through PD-1 and (3) elucidate the functional and physiological consequence of PD-L2
mediated inhibition of T cell function.

16
Chapter 2: Methodology
2.2. Cell lines
Chinese Hamster Ovarian (CHO) cells expressing anti-CD3 protein on the surface and PD-1
expressing Jurkat T cells with a luciferase gene under the control of the NFAT response
element (NFAT-RE) were purchased from the Promega Corporation as part of the PD-1/PD-
L1 Blockade Bioassay. The CHO cells were retrovirally transduced to overexpress human
RGMb, PD-L1 alone, human PD-L2 alone and both human PD-L1 and PD-L2. The cells were
bulk sorted by flow cytometry for surface level PD-ligand expression.
The mesothelin specific CAR-T cells and 3T3 cells overexpressing mesothelin were a gift from
Dr. Pawel K. Mazur lab (UT MD Anderson Cancer Center, Houston, TX). The murine glioma
cell line GL261 was a gift from Amy Heimberger lab (UT MD Anderson Cancer Center,
Houston, TX). The murine cancer cell lines and human cancer cell lines from Figure1 were
purchased from American Type Culture Collection (ATCC; Manassas, VA).
The lentiviral plasmid vector carrying Cas9 and gRNA targeting human PD-1 were purchased
from GeneCopoeia Inc (Rockville, Maryland) and transiently transfected into Jurkat T cells.
The transfected cells were sorted by flow cytometry for lack of PD-1 expression on the surface.
We tested the PD-1 knock-down Jurkat T cells for surface expression of PD-1 after activation
with CD3/CD28 to ensure knock down of endogenous PD-1. The plasmid vectors for the
mutant forms of PD-1 were purchased from Genscript Biotech Corp (Piscataway, NJ) and
retrovirally transduced in PD-1 knock-down Jurkat cells.

17
2.2. Quantification of PD-ligands expression
We assessed the surface expression of PD-L1 and PD-L2 in murine and human cancer cell
lines by flow cytometry. The cytokines used in the experiment were purchased from
PeproTech and reconstituted according to manufacturer’s instructions. We quantified the
number of PD-ligand molecules on the surface of retrovirally transduced CHOs by using PE
quantibrite beads purchased from BD Biosciences.
2.3. NFAT-RE Reporter Cell Assay
All bioluminescence assays were conducted according to manufacturer’s protocols (Promega
PD-1/PD-L1 Blockade Bioassay). In short, CHO cells expressing the indicated PD-ligands
were grown, counted and plated at a concentration of 4X10⁴cells/well in a 96-well flat bottom
(white) plates. The cells were allowed to adhere to the surface of the plate overnight and the
following day Jurkat T cells were harvested, washed and counted and added to the wells
containing CHO cells at a concentration of 5X10⁴cells/ well. The indicated antibodies were
titrated and added to the well accordingly. The cells were incubated for 6 hours at 37ºC. At
the end of the incubation time Bio-Glo reagent was added to the wells and the luminescence
was measured using a luminometer (Schematic 1). Dr. Chantale Bernatchez was kind
enough to allow us to use her laboratory’s luminometer. The same experimental set up was
used to study the impact of PD-ligands on Jurkat T cells expressing mutant forms of PD-1 on
the surface.
2.4. Cytometric Bead Array
The cytometric bead array was performed according to manufacturer’s protocols (BD
Cytometric Bead Array Human Th1/Th2/Th17 Cytokine Kit) to quantify the levels of cytokines
in the supernatant of our co-culture experiments. In short, the human TH1/Th2/Th17 cytokine
standards were reconstituted and titrated in assay diluent and mixed with PE detection
18
reagent. The volume of capture beads corresponding to each of 7 cytokines required for the
assay was calculated and mixed. The supernatants from the co-culture experiments were
harvested to be cell-free and mixed with the capture beads in a 1:1 ratio. The supernatants
were then incubated at room temperature for 3 hours on a dry surface before acquiring the
samples by flow cytometry.
2.5. PDL2-RGMb Interaction Assay
We purchased recombinant human RGMb protein from Sino Biological Inc. (USA) and
recombinant human PD-L2 Fc chimera protein from R&D Systems. 293T and CHO cells were
retrovirally transduced to overexpress RGMb(His Tag) protein on the surface. We tested the
ability of recombinant RGMb and PDL2 to interact with the surface of CHO-PDL2 and 293T-
RGMb cells, respectively. The recombinant protein was detected by secondary antibodies
against the His tag and Fc region. We also assessed the interaction between RGMb and PDL2
using NTA-Atto 488 conjugates that specifically bind to His-tag. The NTA-Atto-488 kit was
purchased from Millipore Sigma.
2.6. Microarray analysis
Microarray analysis was performed on total RNA isolated from Jurkat T cells after co-culture
with CHO cells overexpressing PD-ligands (Schematic 1) using the RNeasy Mini Kit (Qiagen)
according to the manufacturer’s instructions. RNA quality was assessed using an Agilent 2100
Bioanalyzer and Affymetrix (ThermoFisher) performed the gene expression profiling. The
robust multi-array average (RMA) was used to normalize raw data from batches using
R/Bioconductor. Differentially enriched genes were identified using the DESeq R package and
filtered using a q value<0.001. We performed pathway analysis using GSEA preranked
platform and filtered differentially regulated pathways using a false discovery rate <0.25.

19
2.7. RPPA Analysis
PD-1+ Jurkat T cells were co-cultured with CHO cells overexpressing the indicated ligands
for 6 hours. After the co-culture the Jurkat T cells were harvested and spun down to remove
contaminating CHO cells and washed twice with cold PBS and dry pellets were stored at -
80ºC. The experiment was performed twice independently, and the cell pellets were sent to
the Proteomic Facility at the Baylor College of Medicine and UT MD Anderson Cancer Center.
We performed a RPPA experiment with pre-activated PBMC isolated human CD4+ and CD8+
T cells co-cultured with CHO cells overexpressing PD-Ligands for 24 hours and the T cells
were harvested and spun down before being flash frozen. The dried cell pellets were sent to
the Proteomics Facility at Baylor College of Medicine. For each pathway considered in the
analysis the members were decided based on literature. The pathway score is then calculated
as the sum of the relative protein level of all positive regulatory members minus that of
negative regulatory members in a particular pathway[123].
2.8. Statistical analysis
Graphical representation and statistical analysis of the data was performed using GraphPad
Prism (Version 8, GraphPad Software, San Diego, CA). Data shown in this dissertation show
mean +/- SD. Sample groups in the experiments were assessed using ANOVA analysis
followed by Tukey’s multiple comparison test. All parametric statistical analysis were
performed based on the assumption of normality and homoscedasticity.

20
Chapter 3: Results
3.1. Mouse PD-L2 does not reflect the immunobiology of human PD-L2
Despite being a higher-affinity binding ligand of the PD-1 co-receptor, PD-L2 is largely
excluded from the arsenal of ICI therapy due to previous failed reports of PDL2 blockade in
transplantable mouse tumor models[89]. The failure of PDL2 blockade to control tumor growth
may be because of its reported T cell co-stimulatory function in mice[124]. Murine PD-L2
(mPD-L2) can co-stimulate CD4+ T cells through the engagement of a second receptor called
Repulsive Guidance Molecule B (RGM-b)[125]. However, the co-stimulatory function of
human PD-L2 (hPD-L2) is often assumed to be like its murine counterpart despite the lack of
any substantial evidence.
Recent reports demonstrated PD-L2 expression across many human tumor tissues and
emphasized the clinical relevance of the ligand as a predictive biomarker of response to α PD-
1 therapy[126]. The widespread expression of PD-L2 on human tumors and its association
with poor prognosis is not accurately reflected by the inefficacy of PD-L2 blockade observed
in mouse models. Hence, we hypothesized that murine PD-L2 does not recapitulate the
underlying biology of human PD-L2 and differs in its function.
In order to investigate the precise function of PD-L2 in humans, we first assessed the surface
expression of PD-L2 on murine and human cancer cell lines through flow cytometry. Murine
tumor cell lines expressed PD-L1 on the surface and upregulated the expression when treated
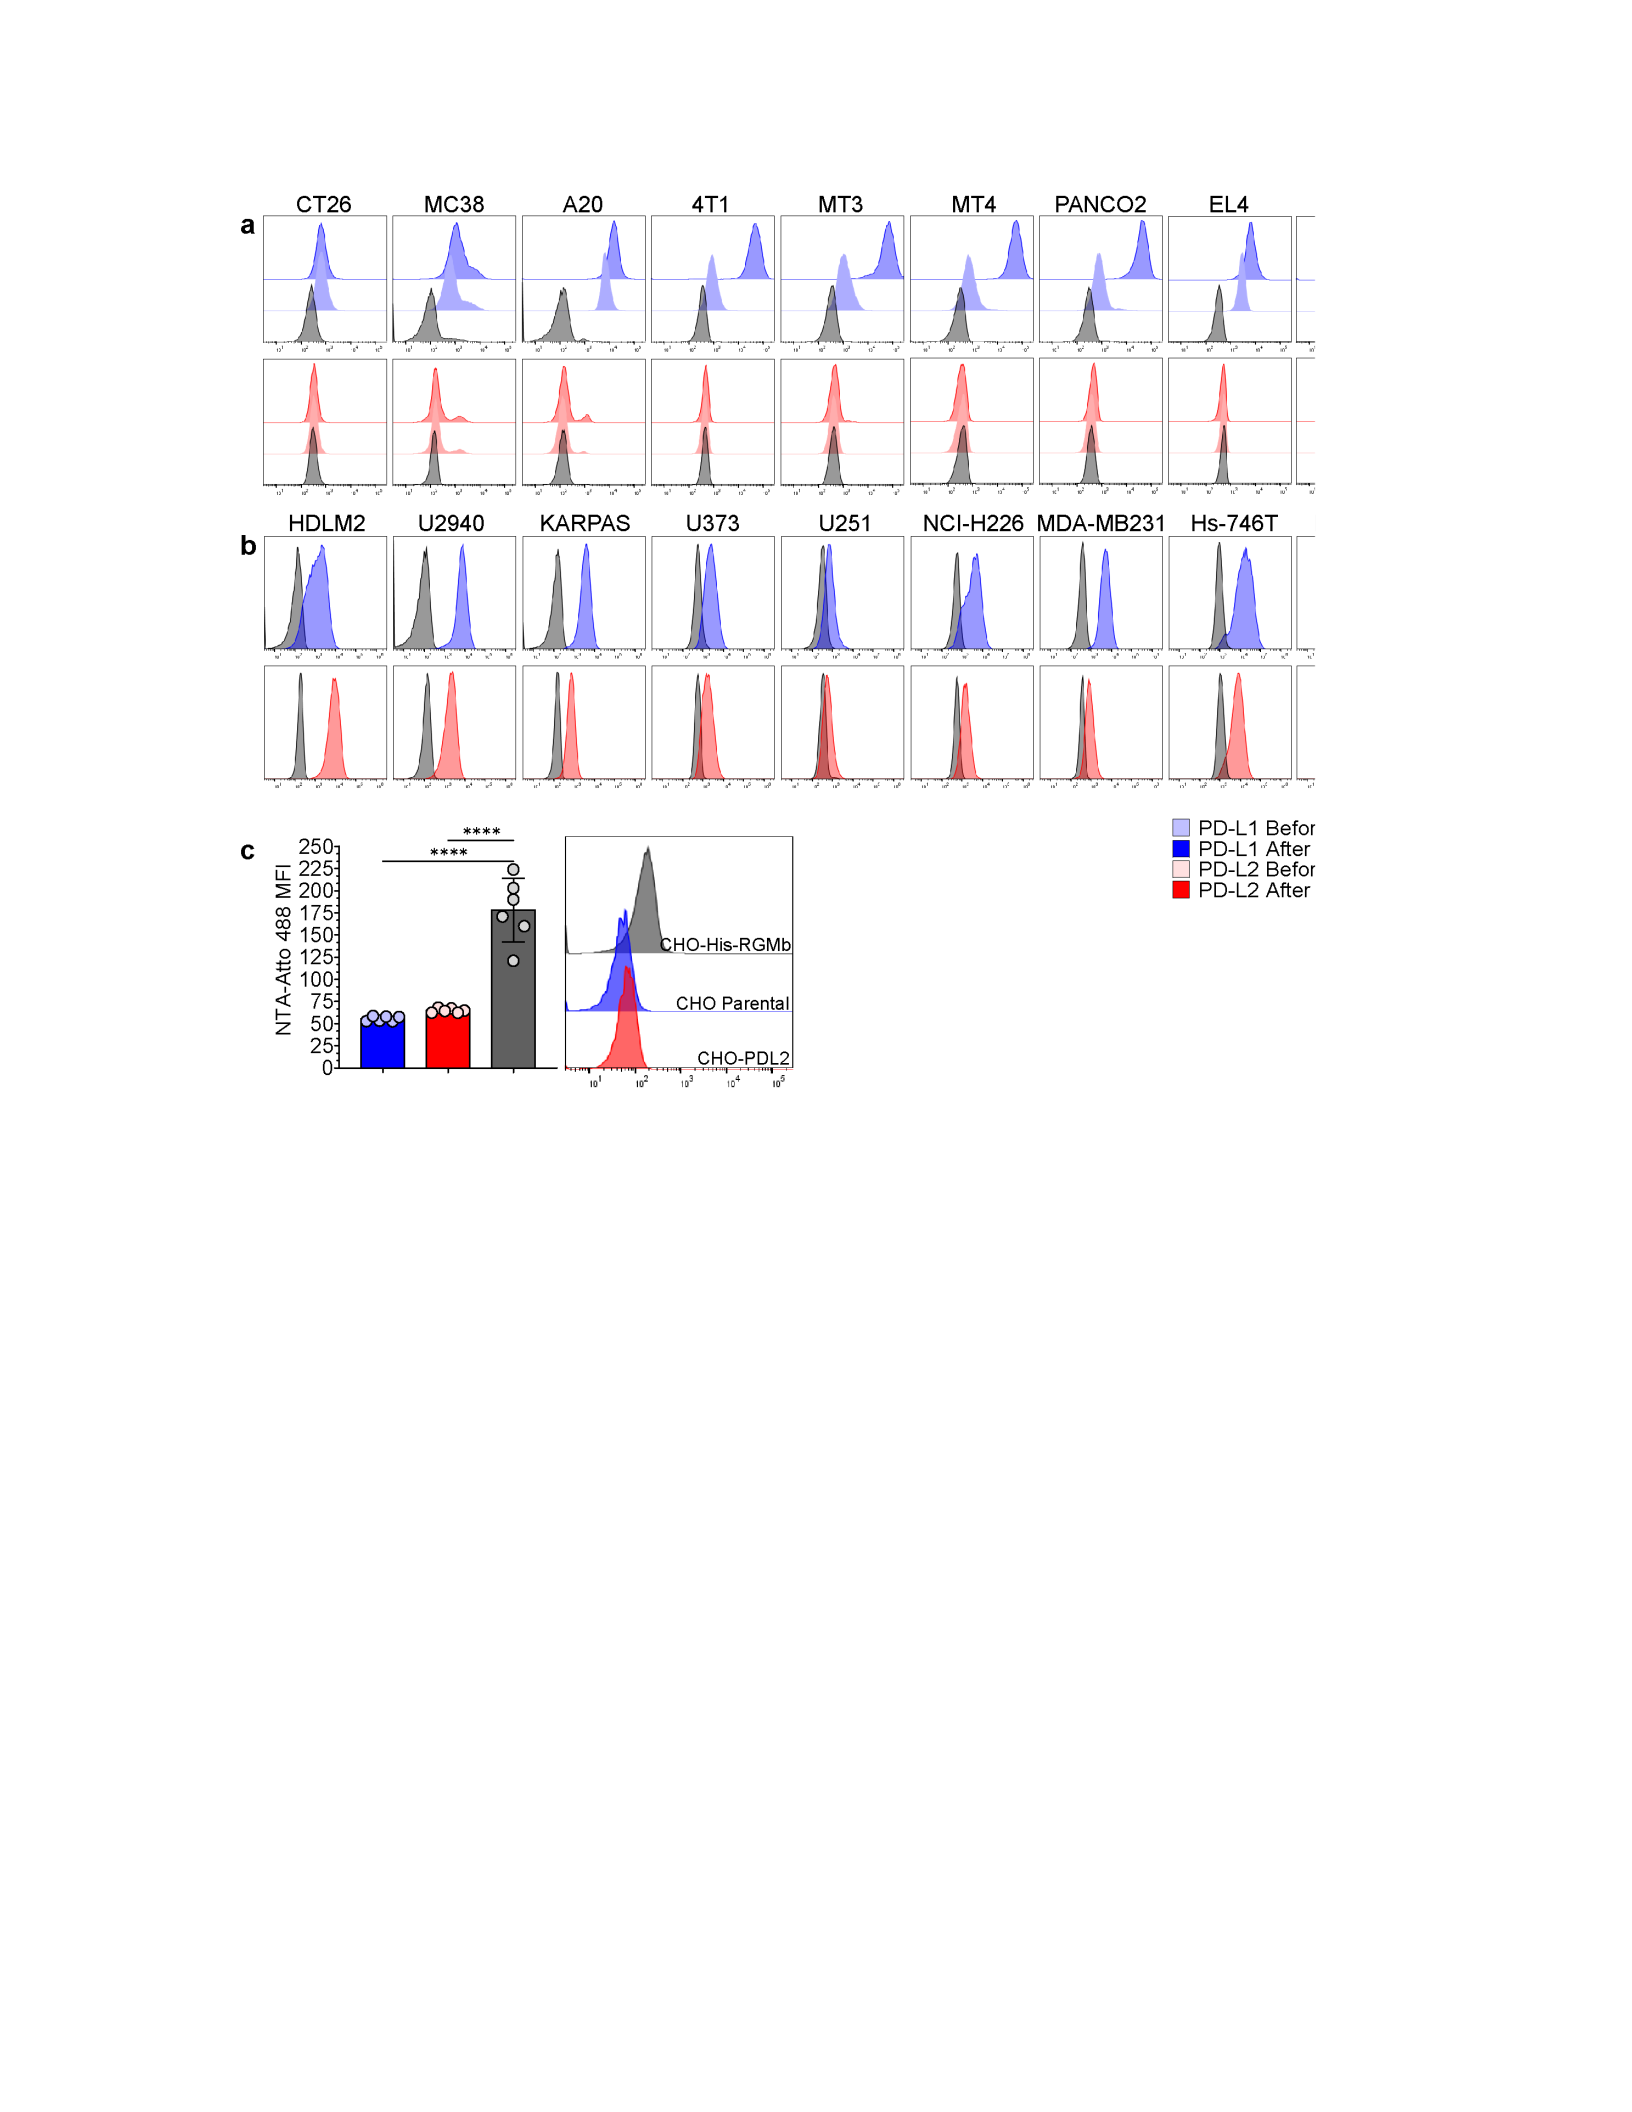
with cytokines like IFNʏ and IL-2 (Figure 1a; Supplemental Fig S1b). We did not observe
any surface expression of PD-L2 on murine tumor cell lines even after induction with
cytokines. Contrary to mouse biology several human tumor cell lines expressed comparable
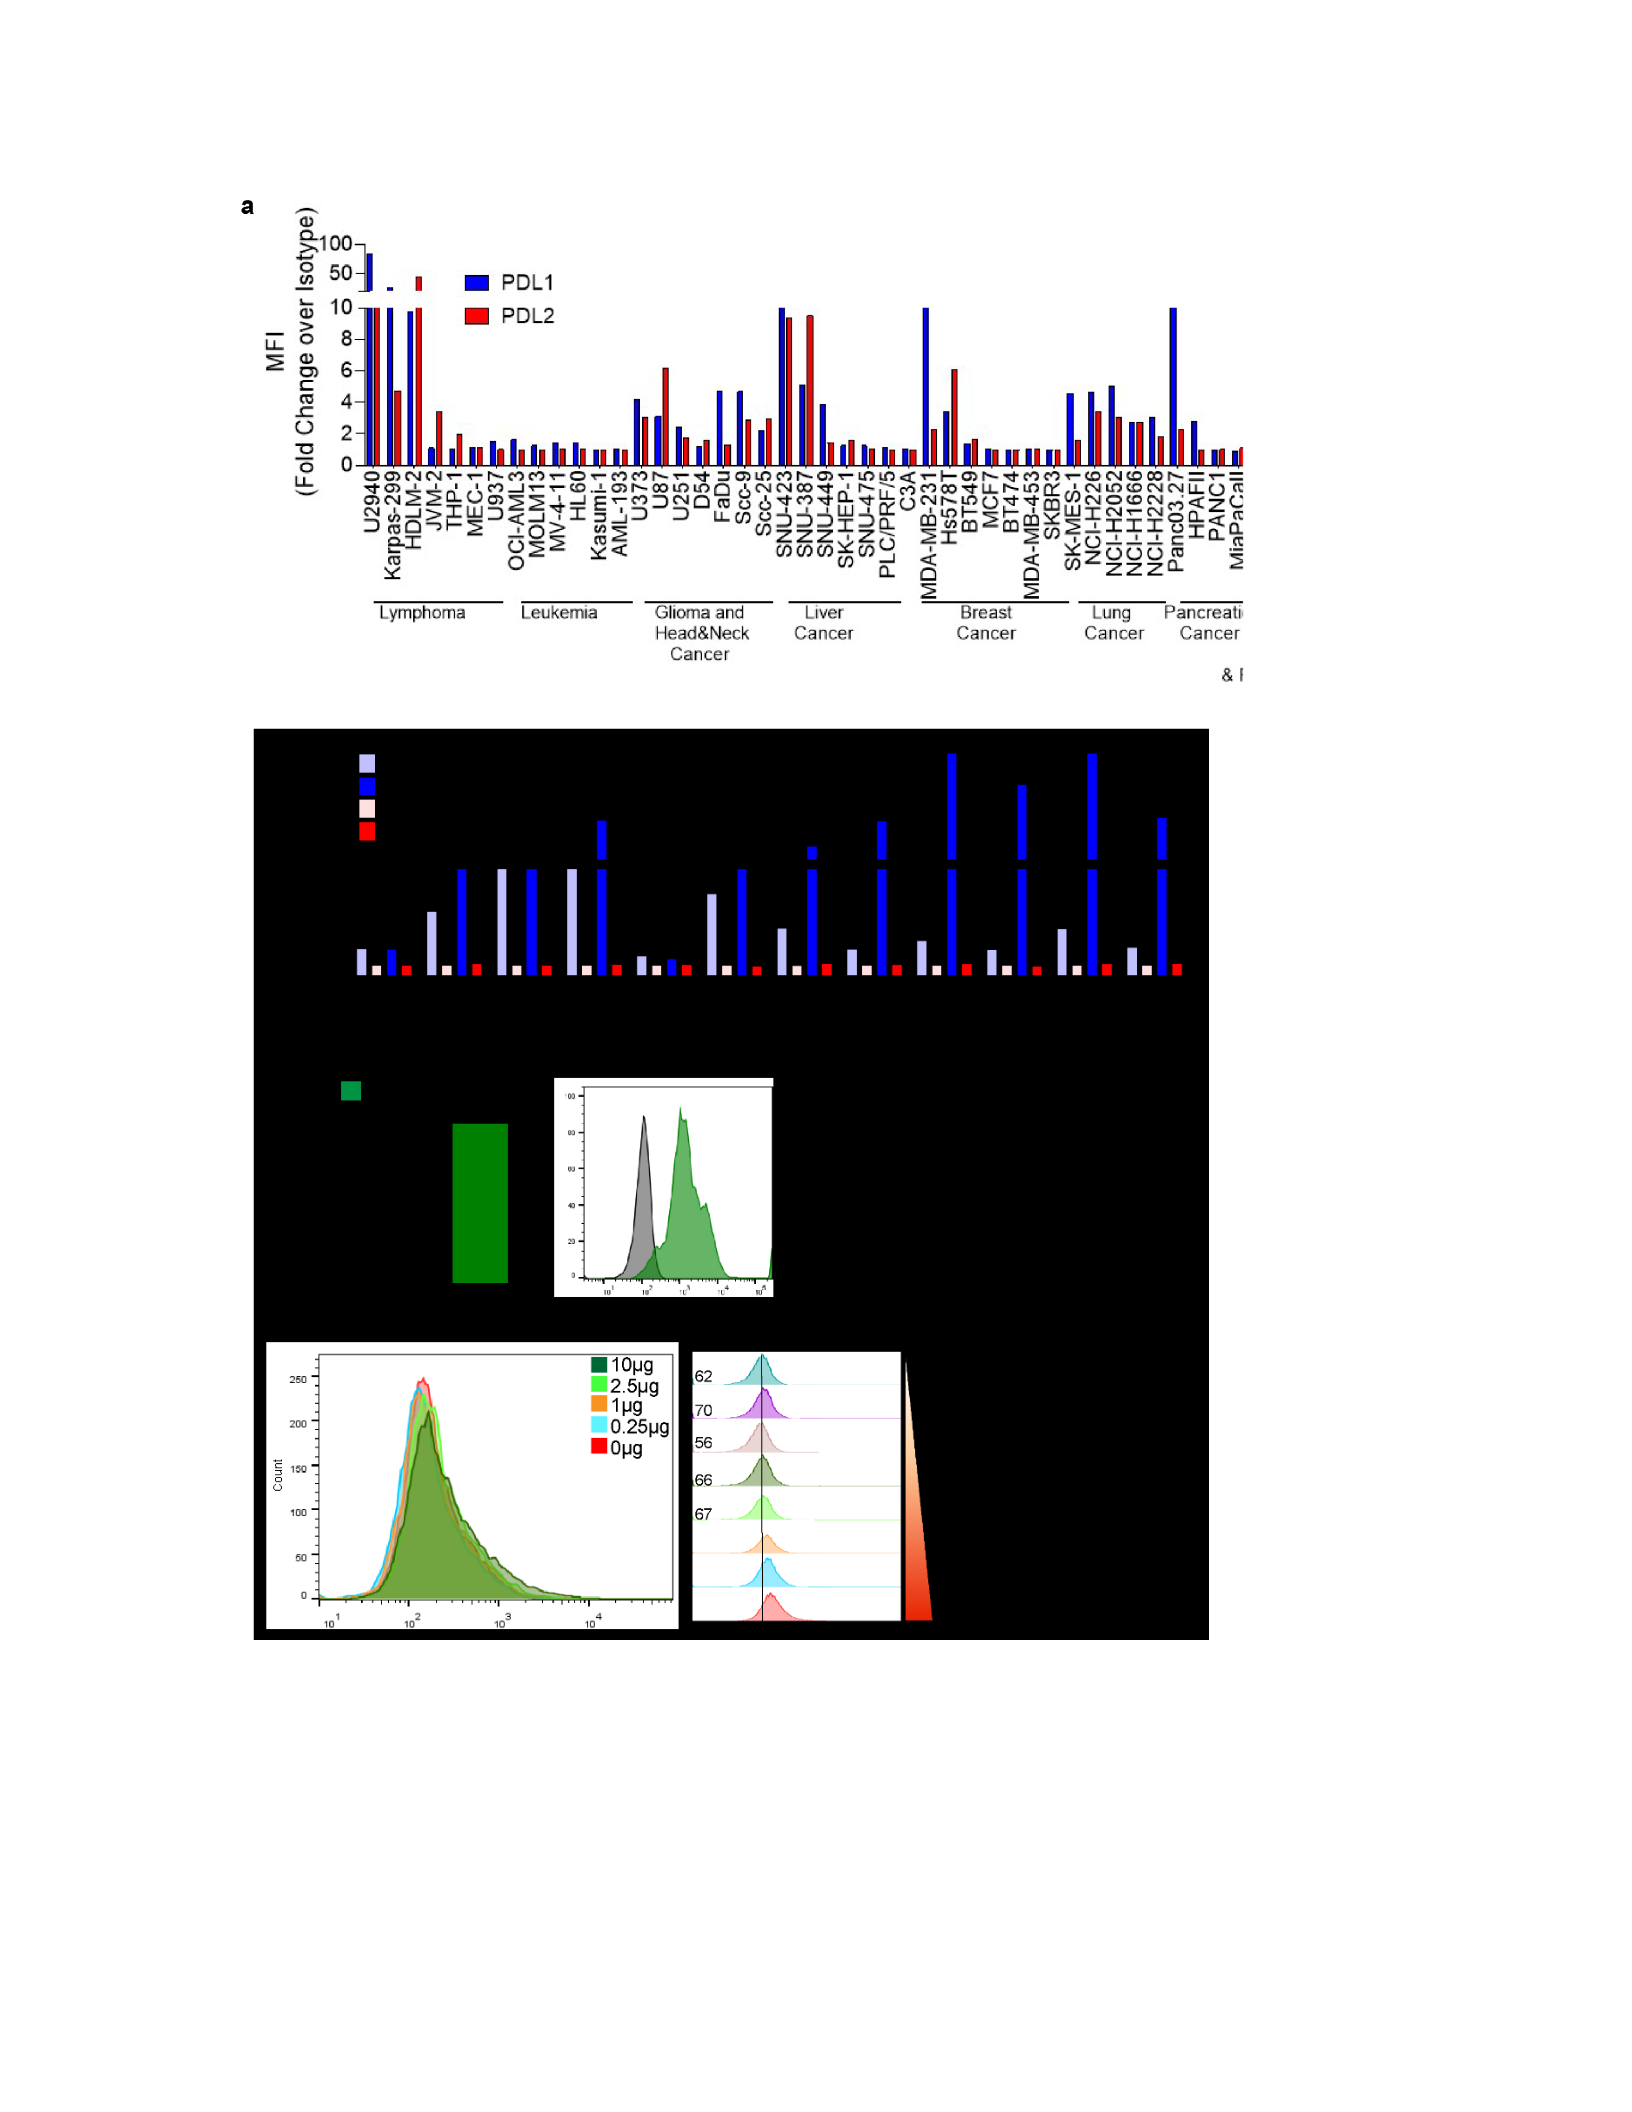
basal levels of PD-L1 and PD-L2 (Figure 1b; Supplemental Fig S1a). Moreover, some
human cancer cell lines like SNU-387 and HDLM-2 showed higher surface expression of PD-

21
L2 than PD-L1 demonstrated by the 2-4 fold increase in mean fluorescence intensity. The
preferential lack of expression of PD-L2 on murine tumor cell lines and widespread expression
of PD-L2 on human tumor cell lines provided preliminary evidence for the possibility of
divergent regulation of PD-L2 in humans and mice.
In order to further emphasize the differences in the function of PD-L2 in mice and humans,
we investigated whether like mPD-L2, hPD-L2 could interact with RGM-b. We tested the direct
binding of hPD-L2 to human RGM-b (hRGM-b) in an in vitro protein-protein interaction assay
and found that recombinant hPD-L2-Fc fusion protein did not bind to 293T cells
overexpressing hRGM-b (Supplemental Fig S1c) on the surface (Supplemental Fig S1d).
However, at the highest concentration tested (10µg) we observed weak binding of His-tagged
hRGM-b recombinant protein to the surface of CHO cells overexpressing hPD-L2 (CHO-
hPDL2). In order to exclude any non-specific binding of anti-His tag secondary antibody, we
validated the interaction between hPD-L2 and hRGM-b in an assay using Ni-NTA-Atto
conjugates that specifically bind to His-tag with minimal cross-reactivity. The Ni-NTA-Atto
conjugates recognized the His-tagged hRGM-b overexpressed on CHO cells and confirmed
the validity of the experimental setup. However, soluble His-tagged hRGM-b recombinant
protein did not specifically bind to the surface of CHO parental and CHO-hPDL2 cells and
hence was not detected by the Ni-NTA-Atto conjugates (Figure 1c).
Our findings showed that PDL2 expression in the context of mouse tumors did not replicate
the expression pattern of human PDL2 and emphasized the possible divergence in the
function of PD-L2 between humans and mouse models. We directly interrogated the
interaction between PD-L2 and RGM-b in humans and found that unlike their mouse analogs,
human PD-L2 does not bind to human RGM-b.
22
Figure 1: Characterization of the biological differences between mouse and human PD-
L2. (a) Surface expression of PD-L1 and PD-L2 across murine cancer cell lines before (light
blue: PD-L1; light red: PD-L2) and after (deep blue: PD-L1; deep red: PD-L2; black:
Unstained) induction with IFNʏ and IL-4 (100µg/ml). (b) Surface expression of PD-L1 and PD-
L2 across human cancer cell lines at the basal level without cytokine inductions (Blue: PD-L1;
Red: PD-L2; Black: Unstained). (c) Mean fluorescence intensity denoting the detection of His-
tagged RGMb protein by Ni-NTA-Atto conjugates.
23
Supplementary Figure S1: Extended data on biological differences between mouse and
human PD-L2. Mean fluorescence intensity denoting the surface expression of PD-L1 and
PD-L2 across human cancer cell lines (a) and murine cancer cell lines (b). (c) Mean
fluorescence intensity denoting surface expression of hRGM-b in 293T cells retrovirally
transduced to overexpress hRGM-b.

24
3.2. Human PD-L2 is solely a co-inhibitory ligand that does not bind RGM-b
We wanted to determine the precise role of hPD-L2 in T cell activation by quantifying the
degree of dephosphorylation in the TCR-CD3 signaling axis mediated via the PD-1 co-
receptor. Since PD-L2 is expressed on several human cancers as observed in our results as
well as in previous scientific literature, we postulated that human PD-L2 is a co-inhibitory
ligand of T cell function and does not retain the co-stimulatory role observed in mice.
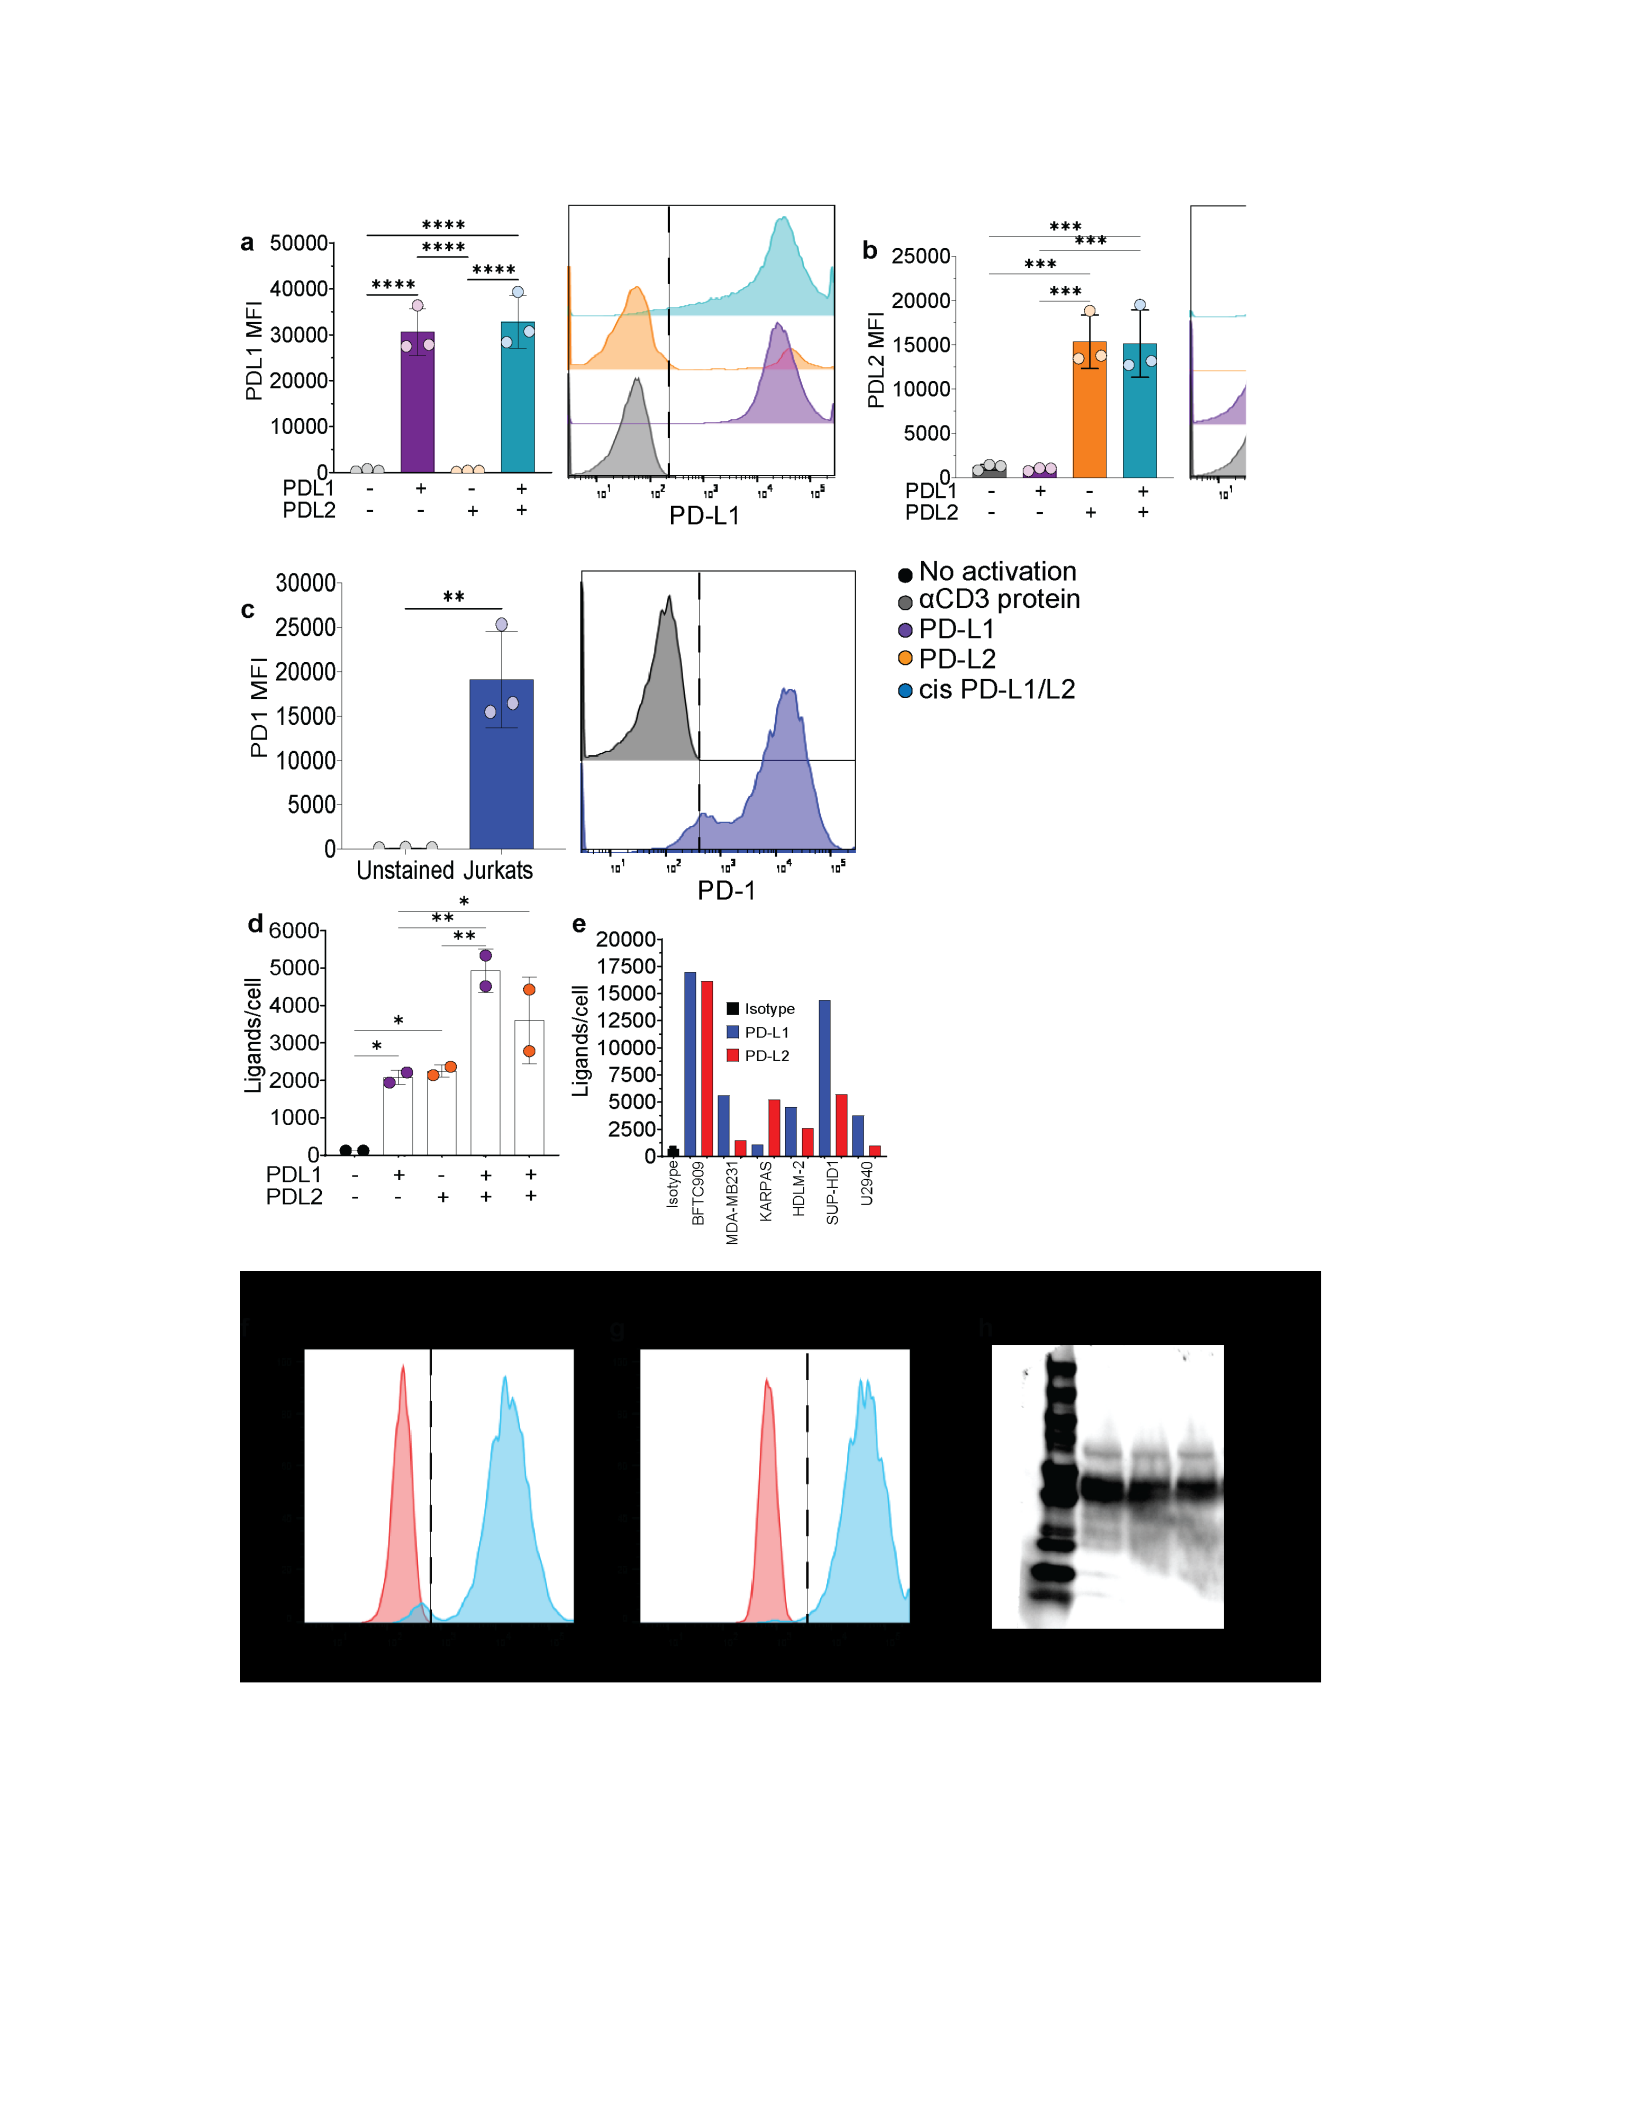
We retrovirally transduced CHO cells to overexpress hPD-L1 alone (CHO-hPDL1), hPD-L2
alone (CHO-hPDL2) and both hPD-L1 and hPD-L2 (CHO-cisPDL1/L2) on the surface
(Supplemental Fig S2a, S2b, S2c). Transduced CHO cells were sorted based on surface
expression of comparable number of PD-1 ligands. We quantified the number of ligands using
PE-quantibrite beads as 2000 ligands on the surface of CHO-hPDL1, CHO-hPDL2 cells and
around 5000 ligands on CHO-cisPDL1/L2 cells (Supplemental Fig S2d). We also quantified
the number of PD-ligands on the surface of human cancer cell lines and found that BFTC-909
expressed ~15,000 ligands of PD-L1 and PD-L2 on the surface, whereas KARPAS expressed
higher number of PD-L2 than PD-L1 ligands on the surface (Supplemental Fig S2e). The
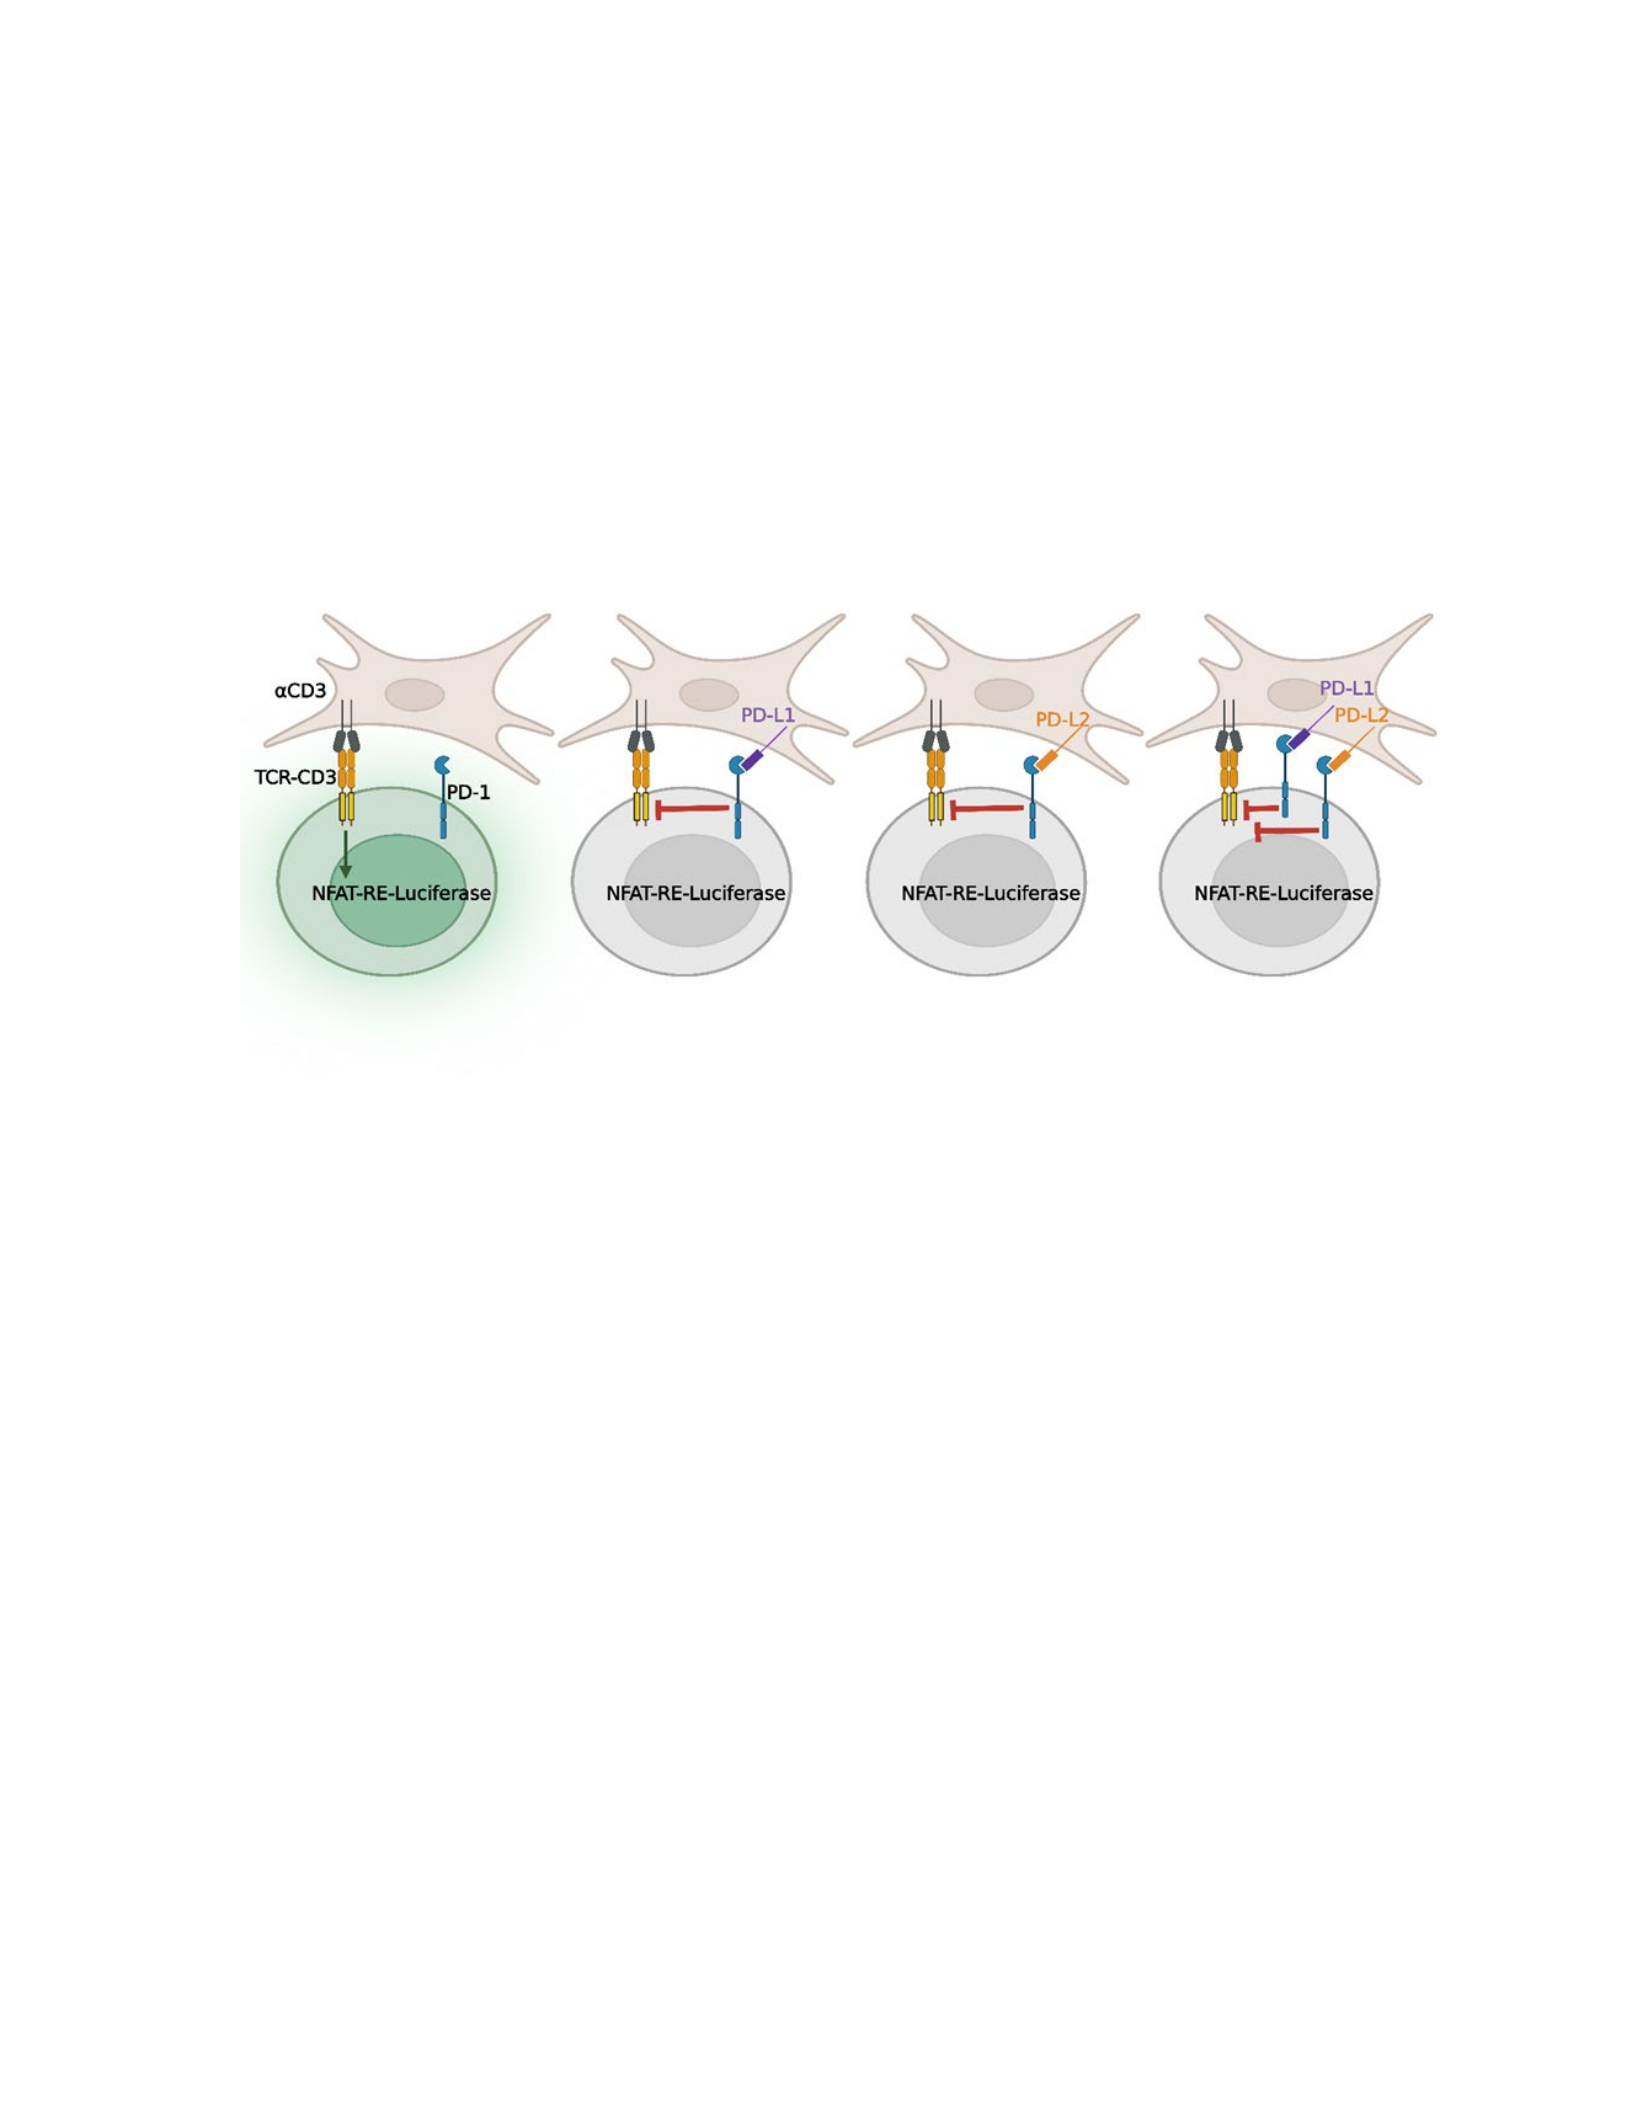
CHO cells also expressed the anti-CD3 scFv protein fragment on the surface that activated
the TCR-CD3 axis in Jurkat T cells, resulting in bioluminescence due to the luciferase reporter
gene under the regulation of the NFAT-response element (RE) (Schematic 1). As a negative
control, we used CHO-S cells that did not express the anti-CD3 protein fragment (No
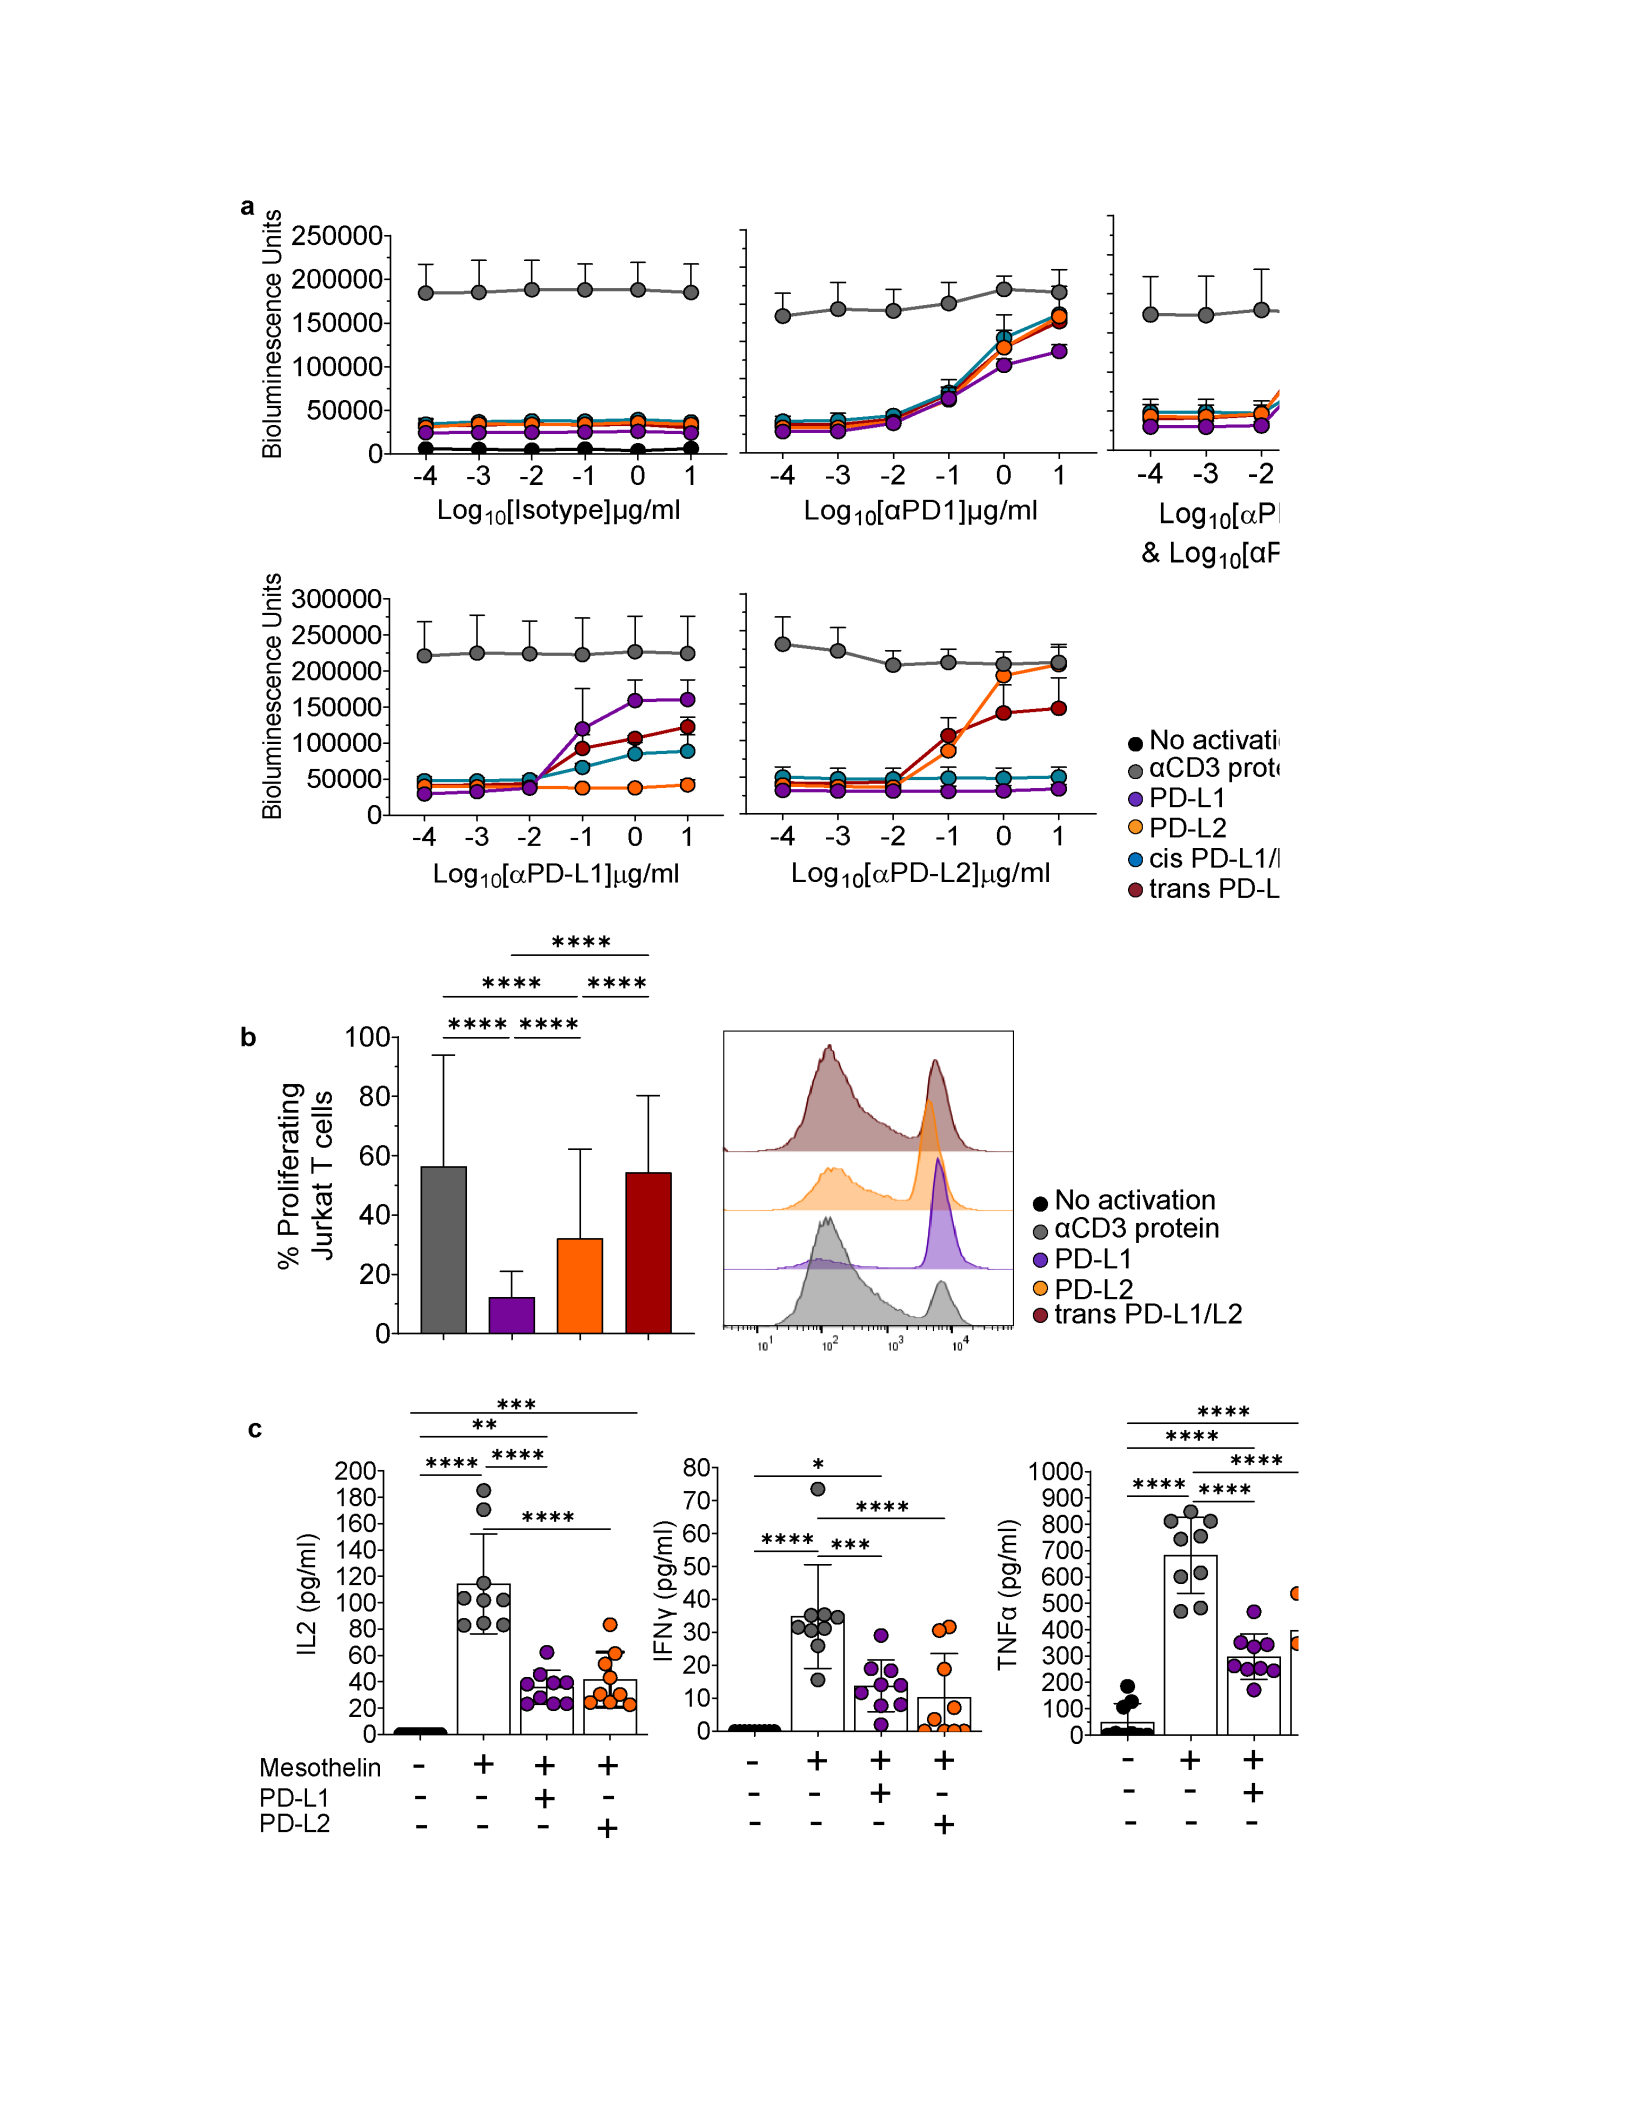
activation). Using this reporter system, we found that CHO-hPDL2 like CHO-PDL1
suppressed T cell activation and did not co-stimulate T cells (Figure 2a). PD-1 blocking
antibody restored T cell activation demonstrated by the increase in bioluminescence and
confirmed that PD-1 on Jurkat T cells mediated the inhibition of the TCR-CD3 axis. Similarly,
anti-PDL1 and anti-PDL2 blocking antibodies showed that it was the specific PD-1/PD-L1 and
PD-1/PD-L2 interaction that inhibited the activation of Jurkat T cells. While PD-L2 blocking

25
antibody completely relieved PD-1/PD-L2 inhibition, it only partially restored inhibition
mediated by a mix of CHO-hPDL1 and CHO-hPDL2 (CHO-transPD-L1/L2: 4X10⁴ cells of
CHO-hPDL1 + 4X10⁴ cells of CHO-hPDL2) since PD-1 continued to interact with PD-L1.
Surprisingly, only PD-L1 blocking antibody and not PD-L2 blocking antibody interfered with
CHO cells co-expressing PD-ligands (CHO-cisPD-L1/L2) inhibition and restored
bioluminescence. The co-expression of PD-L1 and PD-L2 on the same cell may have resulted
in cis-interaction between the ligands such that inhibition via PD-1 was primarily driven by PD-
L1. As expected, PD-L1 blocking antibody efficiently relieved inhibition by CHO-PDL1 as well
as CHO-cisPD-L1/L2 and partially CHO-transPD-L1/L2. The combinatorial blockade of PD-
L1 and PD-L2 replicated the data observed in the mono-blockade of PD-1.
In addition to the influence of PD-ligands via PD-1 on membrane proximal signaling events,
we also tested the effect of PD-L2 on human T cell proliferation and cytokine production. We
co-cultured CFSE stained Jurkat T cells with CHO-hPDL1, CHO-hPDL2 and CHO-transPD-
L1/L2 for 72 hours and assessed the dilution of CFSE by flow cytometry (Figure 2b). CHO-
hPDL1 inhibited proliferation of Jurkat T cells efficiently but CHO-hPDL2 appeared to have a
less potent effect in the experiment. CHO-transPD-L1/L2 exhibited a null effect as the higher
affinity of PD-L2 out-competed PD-L1 to bind to PD-1. The increased proliferation induced by
CHO-transPD-L1/L2 compared to CHO-hPDL2 may be due to the increased number of CHO-
transPD-L1/L2 cells (8X10⁴) used in the experiment, resulting in a 2X engagement of the TCR-
CD3 complex by the αCD3 protein expressed on the CHO cells. We ensured to maintain the
CHO cell number at 4X10⁴ across all the samples in our following experiment. We also
validated the inhibitory function of PD-L2 during antigen-specific T cell activation. We showed
that CAR-T cells in the presence of PD-ligands produced significantly lower amounts of pro-
inflammatory cytokines like IL-2, IFN-g and TNFa when activated by its corresponding antigen
mesothelin for 72 hours (Figure 2c).
26
Taken together, our data demonstrated that human PD-L2 is exclusively a T cell co-inhibitory
ligand that binds to the PD-1 co-receptor to inhibit T cell cytokine production and NFAT-
mediated T cell activation. However, PD-L2/PD-1 binding inhibited the proliferation of T cells
to a lesser extent than PD-L1 and appeared to be a weaker inhibitory ligand of PD-1 at least
at the level of proliferation.
Schematic 1: Representation of the bioluminescent assay to characterize the nature of
regulation mediated by PD-L1 and PD-L2 through PD-1 when Jurkat T cells are activated via
TCR-CD3 complex.
w”)
‘€
250000
>
g
200000;
$$
B
150000
2
100000
§
50000
2
ao
0
T T T T T
T
T
T
T T T T
4-3-2
-1
0
1
4
-3
-2
-1
0
1
4
-3 -2
-1
0
1
Log,o[Isotype]yg/ml
Logiof[aPD1]yg/ml
Logio[aPD-L1]ug/ml
&
Log,
[aPD-L2]
g/ml
=
300000
@
250000
©
200000
2
150000
=
100000
@
No
activation
=
50000
e@
aCD3
protein
2
0
@PD-L1
4-3-2
-1
0
1
4-3
-2
-1
0
1
Sie
pO
Te
@cis
-
Log4o[aPD-L1]ug/ml
Log
4o9[aPD-L2]ug/ml
e
trans
PD-L1/L2
KKK
KKK
2
AK
KK
b
100;
KKK KKK
2
801
=
oOo
oO
SE
60
2
S
]
e
No
activation
at
40
e@
aCD3
protein
SP
46)
@
PD-L1
©
PD-L2
0
|
@trans
PD-L1/L2
2K
K
KK KK
c
**
RK
200,
*#**
“STE
80)
__*
1000,
“ee
180}
°
70:
©
pee
goo]
~~"
****
_
160;
a
=
604
kr
=
800;
@|e@
=
1404
E
—
ee
=
700;
5
1201
30)
&
600]
[ee
@
&
1004
=
404
%
«900;
@®|
e@
N
80;
®@®
2
30:
e
@®
t&
400;
=
ue
=
3004
Mesothelin
-—-
PD-L1
-
PD-L2
- -
1
+
+
60-
@
=
40}
Se
OW
wt
200]
2
204
100]
@
0
v T T
04
0
T T
+ +
+
-
-
+
I++
I
I
1+,
C++
I
27

28
Figure 2: PD-L2 is solely a T cell co-inhibitory ligand in humans. (a) 4X10⁴ CHO cells
overexpressing indicated proteins and 5X10⁴ PD-1+ Jurkat T cells (NFAT-RE-Luciferase
reporter) were co-cultured for 6 hours with a titration of indicated immune checkpoint blockade
antibodies. TCR-CD3 activation was measured by luciferase assay according to
manufacturer’s instructions and represented as bioluminescence units. (b) PD-1+ Jurkat T
cells were co-cultured with indicated CHO cells overexpressing PD-Ligands for 72 hours and
proliferation was quantified by dilution of CFSE stain. (c) Mesothelin specific CAR-T cells were
co-cultured with 3T3 cells overexpressing mesothelin, PD-L1 and PD-L2 for 72 hours and pro-
inflammatory cytokines levels (IL-2, IFNʏ and TNFα) in the supernatant were measured by
Cytokine Bead Array. Statistical significance was calculated using a one-way ANOVA. *p<
0.05, **p<0.01, ***p<0.001, ****p<0.0001.
29

30
Supplementary Figure S2: Extended data on the T-cell co-inhibitory function of human
PD-L2. (a)(b) CHO cells expressing the αCD3 protein were retrovirally transduced to
exclusively express PD-L1 (CHO-hPDL1), PD-L2 (CHO-hPDL2) and co-express both the
ligands (CHO-cis-PD-L1/L2) and assessed for surface expression by flow cytometry. (c) Mean
fluorescence intensity of PD-1 expression on the surface of Jurkat T cells. (d) The number of
PD-L1 and PD-L2 molecules on the surface of CHO cells after retroviral transduction and (e)
human cancer cell lines at the basal level are shown. (f) Expression of human PD-L1 and (g)
human PD-L2 on the surface of 3T3 cells by flow cytometry. (h) Western blot of mesothelin in
whole cell lysates of 3T3 cells. Statistical significance was calculated using a one-way
ANOVA. *p< 0.05, **p<0.01, ***p<0.001, ****p<0.0001.

31
3.3. Human PD-L2 binds PD-1 to induce a unique transcriptional program in Jurkat T
cells
The unique biophysical properties of the PD-1/PD-L2 interaction and its restricted expression
pattern on antigen presenting cells (APCs) and the female reproductive tract as opposed to
the widespread expression of PD-L1 on inflamed tissues strongly indicate towards a possible
nonredundant role of PD-L2 in humans[61,89]. Furthermore, NMR simulation studies of the
extracellular domain of PD-1 elucidated that the PD-ligands bind to the same region on human
PD-1 in seemingly different ways such that PD-L2 formed a smaller interface than PD-L1 to
make the PD-1/PD-L2 complex more stable than the PD-1/PD-L1 complex. We wanted to
investigate whether the differential engagement of PD-1 by its ligands can result in distinct
signaling mechanisms downstream of PD-1. Hence, we hypothesized that human PD-L2
binds to PD-1 to induce an inhibitory mechanism via PD-1 that is different from PD-L1.
While it is known that PD-1 on binding to PD-L1 recruits SHP-2 to attenuate T cell activation,
it was only recently appreciated that PD-1 can also reprogram the transcriptome of an
activated T cell by inhibiting the upregulation of distinct sets of T cell effector genes
[57,67,69,127]. Even though this study was seminal in elucidating the nuanced mechanism of
PD-1 inhibition, much like the body of research before it, the study ignored the role of PD-L2
in PD-1 mediated T cell inhibition.
With an aim to comprehensively study the PD-1 signaling axis we evaluated the genetic
program induced by PD-1 when bound to PD-L1 or PD-L2 using the Jurkat-CHO system
(Schematic 1). We co-cultured Jurkat T cells with each type of adherent CHO cell transduced
to express PD-ligands (CHO-hPDL1, CHO-hPDL2, CHO- cis-CHOPDL1/L2 and trans-
CHOPDL1/L2) for 6 hours and harvested bulk RNA to generate Affymetrix microarray data.
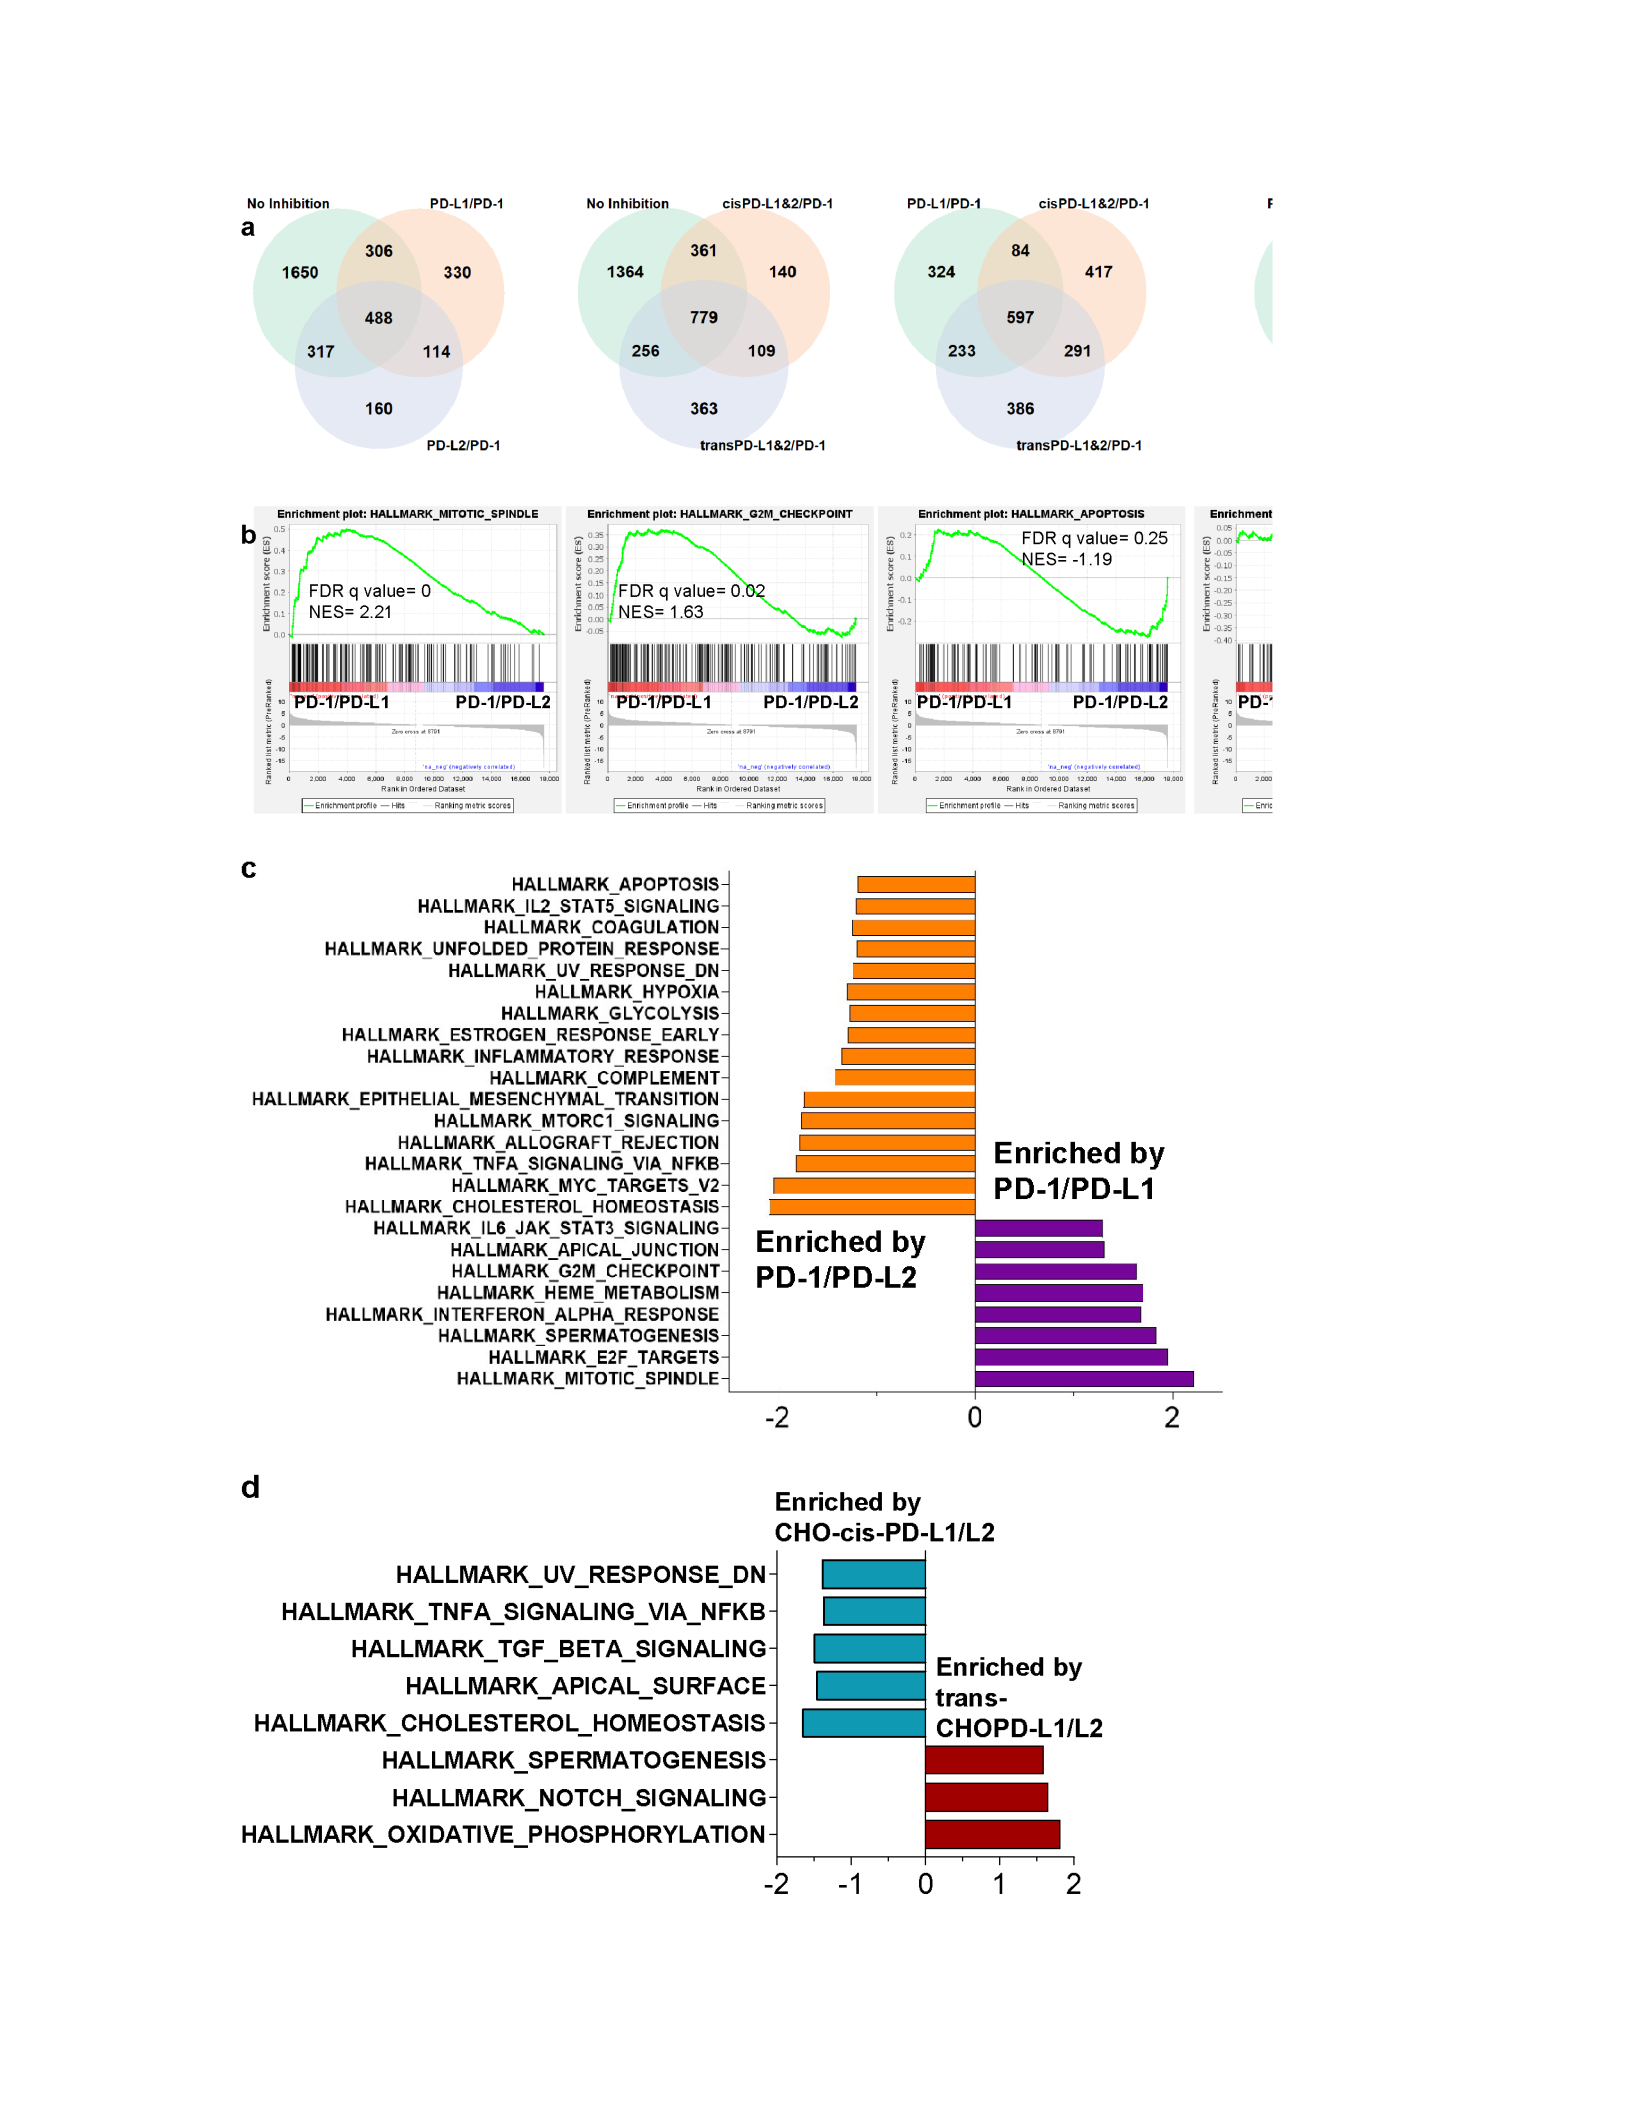
A venn diagram depicting the overlap of differentially enriched genes (adj.p.value<0.05)
identified a transcriptional program of 160 genes and 330 genes that were unique to PD-1/PD-

32
L2 and PD-1/PD-L1 meditated inhibition, respectively (Figure 3a). To gain more insight into
the physiological relevance of this unique signature we performed Gene Set Enrichment
Analysis (GSEA) (Figure 3c). We observed significant differences in the molecular pathways
regulated by PD-L1 and PD-L2. Hallmark pathways associated with T cell activation like TNFa
Signaling via NFKB, MTORC1 signaling, and Glycolysis were selectively enriched by PD-L2
when compared to PD-L1. We also found cell proliferation related gene sets like G2M
checkpoint, E2F Targets and Mitotic Spindle downregulated by PD-L2 versus PD-L1 (Figure
3b). Our findings suggest that PD-L1 inhibits T cells through the downregulation of pathways
like MTORC1 (downstream to PI3K/Akt pathway) resulting in a transcriptomic signature
aligned with previous studies in the field. However, PD-L2 did not follow the same mechanism
and instead preferentially impacted cell cycle associated pathways. Some of the DEGs that
contributed to the core enrichment of the differential pathways were the upregulation of
BCL2L1L, MXD3, PIFI, KIF2A, KIF3B and SDC2 and the downregulation of FBXO5, IRF1,
IFI35, TAP1, PEA15, SQLE, DHCR24, EBP, MXD3 and FADS1. While dissecting the
differences between PD-L1 and PD-L2 we found that PD-L2 binding to PD-1 significantly
enriched MYC targets and Apoptosis pathways. This was the first time induction of apoptosis
was observed with PD-1/PD-L2 mediated inhibition. T cell activation, inhibition and activation
induced cell death (AICD) is regulated by a fine balance of molecular signaling. Further studies
to confirm the direct correlation between PD-1/PD-L2 signaling and apoptosis are warranted.
We also observed differentially enriched genes in Jurkat T cells exposed to PD-ligands
expressed in cis or trans to each other, however they did not translate into dramatic
differences in the regulation of molecular pathways in the GSEA results (Figure 3d). This
supported our earlier speculation that PD-L1 and PD-L2 when co-expressed on the same cell
may form heterodimers that retain binding affinity to PD-1. Members of the B7 family of
proteins mediate several non-linear protein-protein interactions and confirmation of a cis
interaction between the PD-ligands will be pivotal to improve therapeutics targeting the PD-1

33
signaling axis. In conclusion the data suggested that the PD-L2 induced a transcriptional
program through the PD-1 co-receptor that is different from PD-L1 to inhibit TCR-CD3
mediated activation. The transcriptional program induced by PD-L2 was less inhibitory in its
phenotype when compared to PD-L1 regulated transcriptional program.
34

35
Figure 3: Characterization of the transcriptional program induced in Jurkat T cells by
PD-1/PD-L1 and PD-1/PD-L2 interactions. (a) Venn diagram showing the overlap of
differentially enriched genes (DEGs; adjusted p value <0.05) between Jurkat T cells inhibited
by hPD-L1, hPD-L2, cis-PD-L1/L2 and trans-PD-L1/L2 through PD-1 in the presence of CD3
activation. (b) Gene set enrichment analysis (GSEA) enrichment plots for the indicated
pathways. The y-axis shows the enrichment score (ES) and the x-axis details the genes
(vertical lines) characteristic of the indicated pathways. The red colored band in the plot
correlates to a high gene expression whereas the blue correlates for a low gene expression.
(c) (d) Bar graphs demonstrating the normalized enrichment score from GSEA analysis
comparing PD-1/PD-L1 inhibited T cells against PD-1/PD-L2 (c) and PD-1/CHO-cis-PD-L1/L2
against (d) PD-1/CHO-trans-PD-L1/L2 inhibition.
36
Pathway
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
Apoptosis
PI3K/Akt
PISK/Akt
PISK/Akt
PI3K/Akt
PISK/Akt
PISK/Akt
PI3K/Akt
PISK/Akt
PISK/Akt
PI3K/Akt
PISK/Akt
PISK/Akt
PI3K/Akt
PISK/Akt
PISK/Akt
PI3K/Akt
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
Ras/MAPK
mTOR
mTOR
mTOR
mTOR
mTOR
mTOR
mTOR
mTOR
mTOR
mTOR
mTOR
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Cell
cycle
Antibody
Bad_pS112
Bak
Bax
Bdl2A1
Bcl2
Bcl-xL
Bid
Bim
Caspase-3
Caspase-7-cleaved
c-IAP2
Akt1_pS473
Akt_p$473
Akt_pT308
GSK-3a-b_pS21_S9
INPP4b
p27_pT198
PRAS40_pT246
PTEN
Tuberin_pT1462
PI3Kp85
PI3KP110A
PI3Kp11b
mTORpS2448
mTOR
pPDK1($241)
PDK1
B-Raf_pS445
c-Jun_p$73
C-Raf_pS338
JNK_pT183_Y185
MAPK_pT202_Y204
MEK1_pS217_$221
p38_pT180_Y182
p9ORSK_pT573
Shc_pY317
YB1_pS102
A-Raf
c-Jun(60A8)_R_V
p38/MAPK_R_V
p44/42MAPK(Erk1/2)_R_V
4E-BP1_pS65
mTOR_pS2448
p70-S6K_pT389
Rictor_pT1135
S$6_p$235_$236
S6_p$240_$244
PRAS40
PRAS40_pT246
Raptor
mTOR
p70-S6K1
Cdc2_pY15
CDK1
Cydin-B1
Cydin-D1
Cycdlin-D3
Cydin-E1
FoxM1
p27_pT198
p27-Kip-1
PCNA
p-AuroraA(T288)/B(T232)/C(T198)_R_V
AuroraB
p21
p53
Weight
-1
PRP PRP
RP RP RP
PRP
RP BP RP RP BP RP RP BP BP RP BP
BPP
BP BP BP
PRP
Pe
PP ee
'
Be
PPR
RP RP
RB
37

38
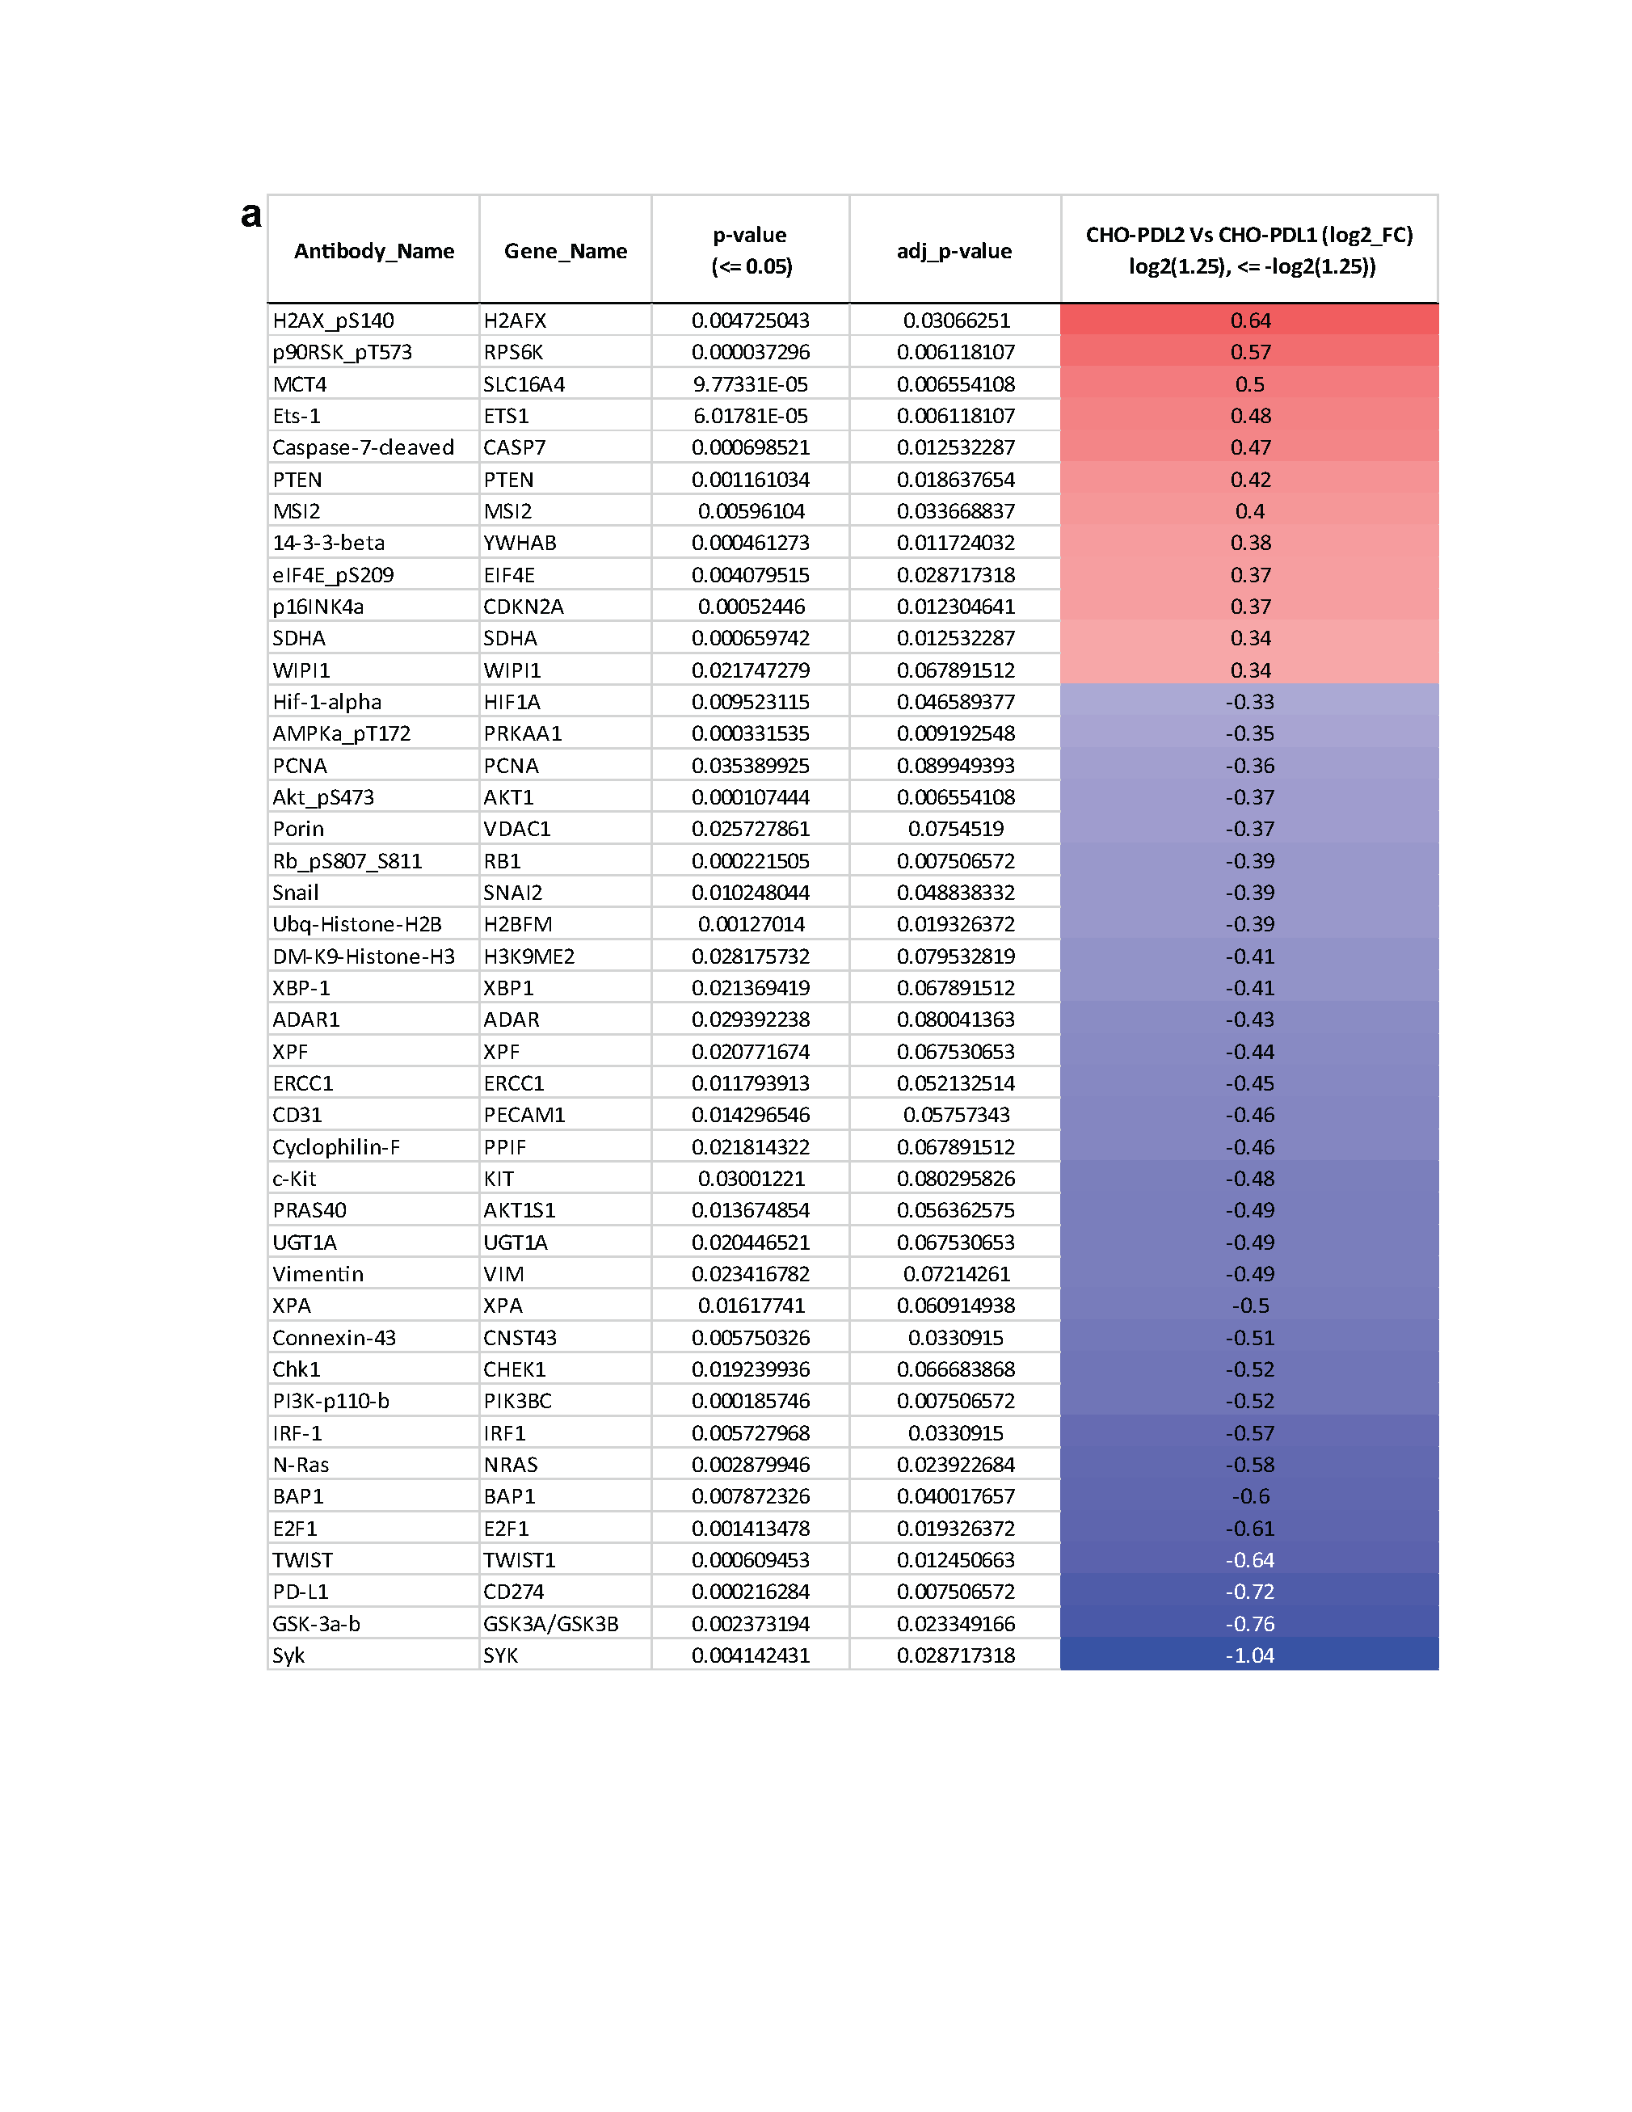
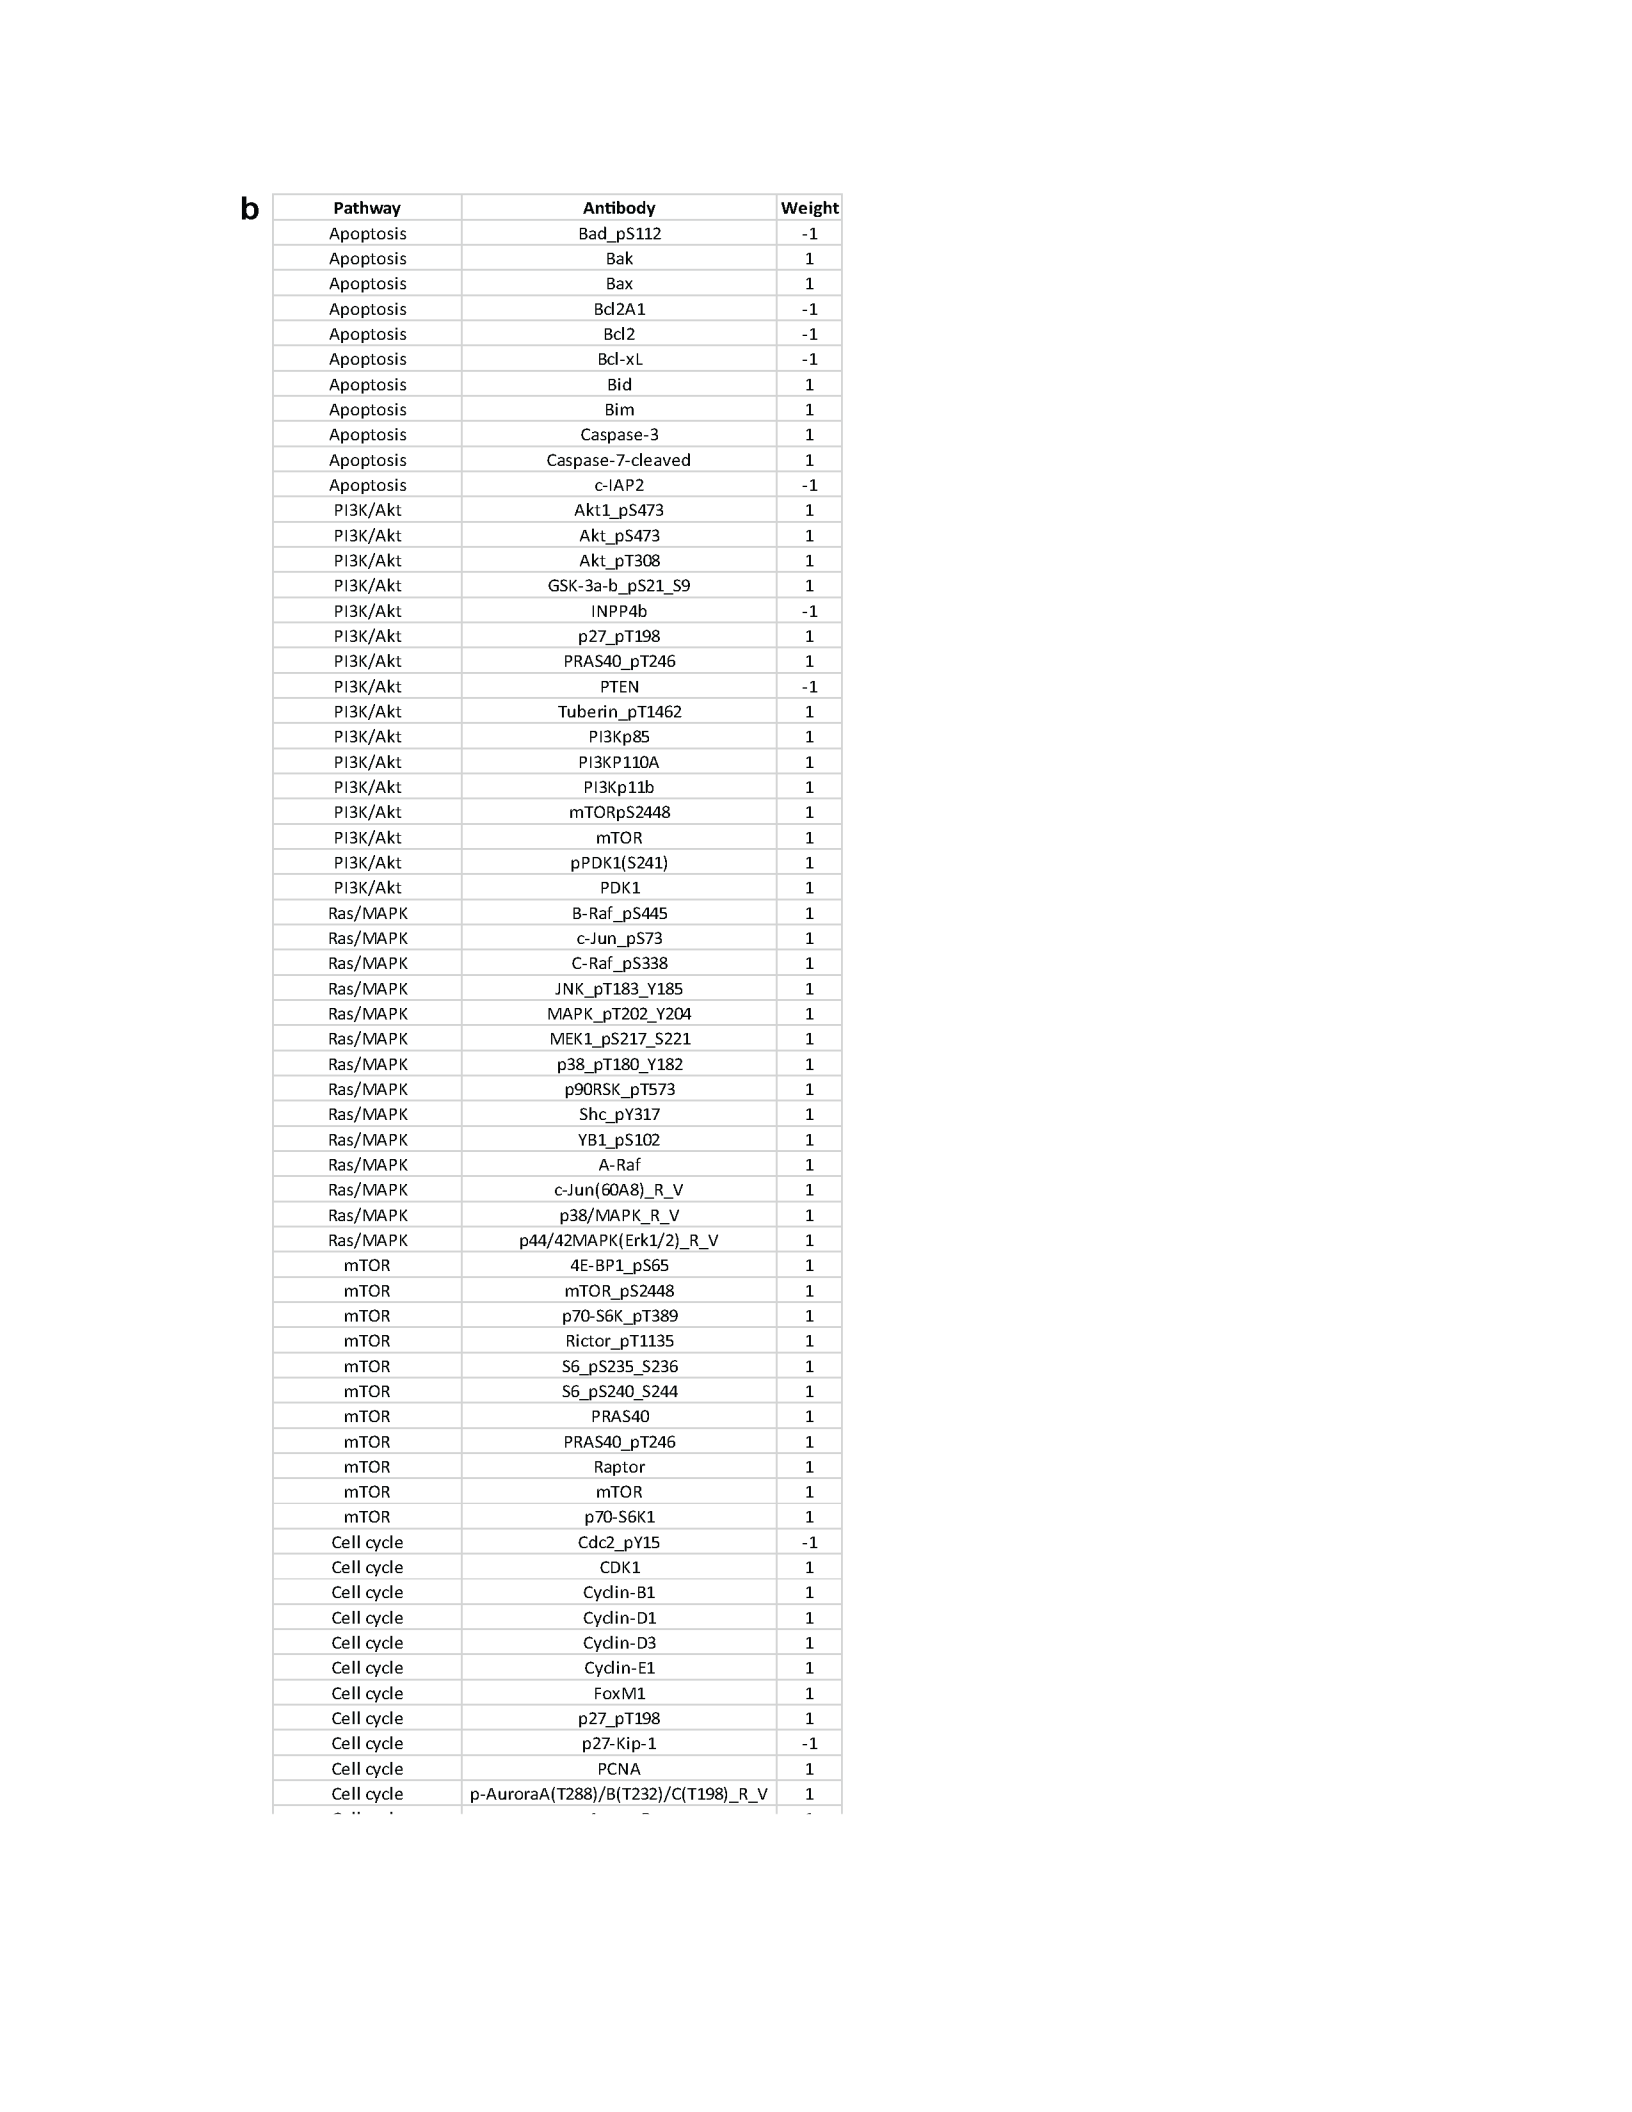
Supplemental Figure S3: Extended data on RPPA analysis. (a) Differentially enriched
proteins when PD-L2 inhibited T cell is compared to PD-L1 inhibited T cells is depicted. (b)
Pathway score membership and the weight assigned to each member protein.

39
3.4. Human PD-L1 and PD-L2 elicit different protein repertoires through PD-1
In addition to the microarray experiment we also assessed the functional differences in the
signaling pathways induced by PD-L1 and PD-L2 through Reverse Phase Protein Array
(RPPA). We used the same co-culture experiment as before and flash froze whole cell pellets
for RPPA. In each sample Jurkats were activated only through the TCR-CD3 axis and
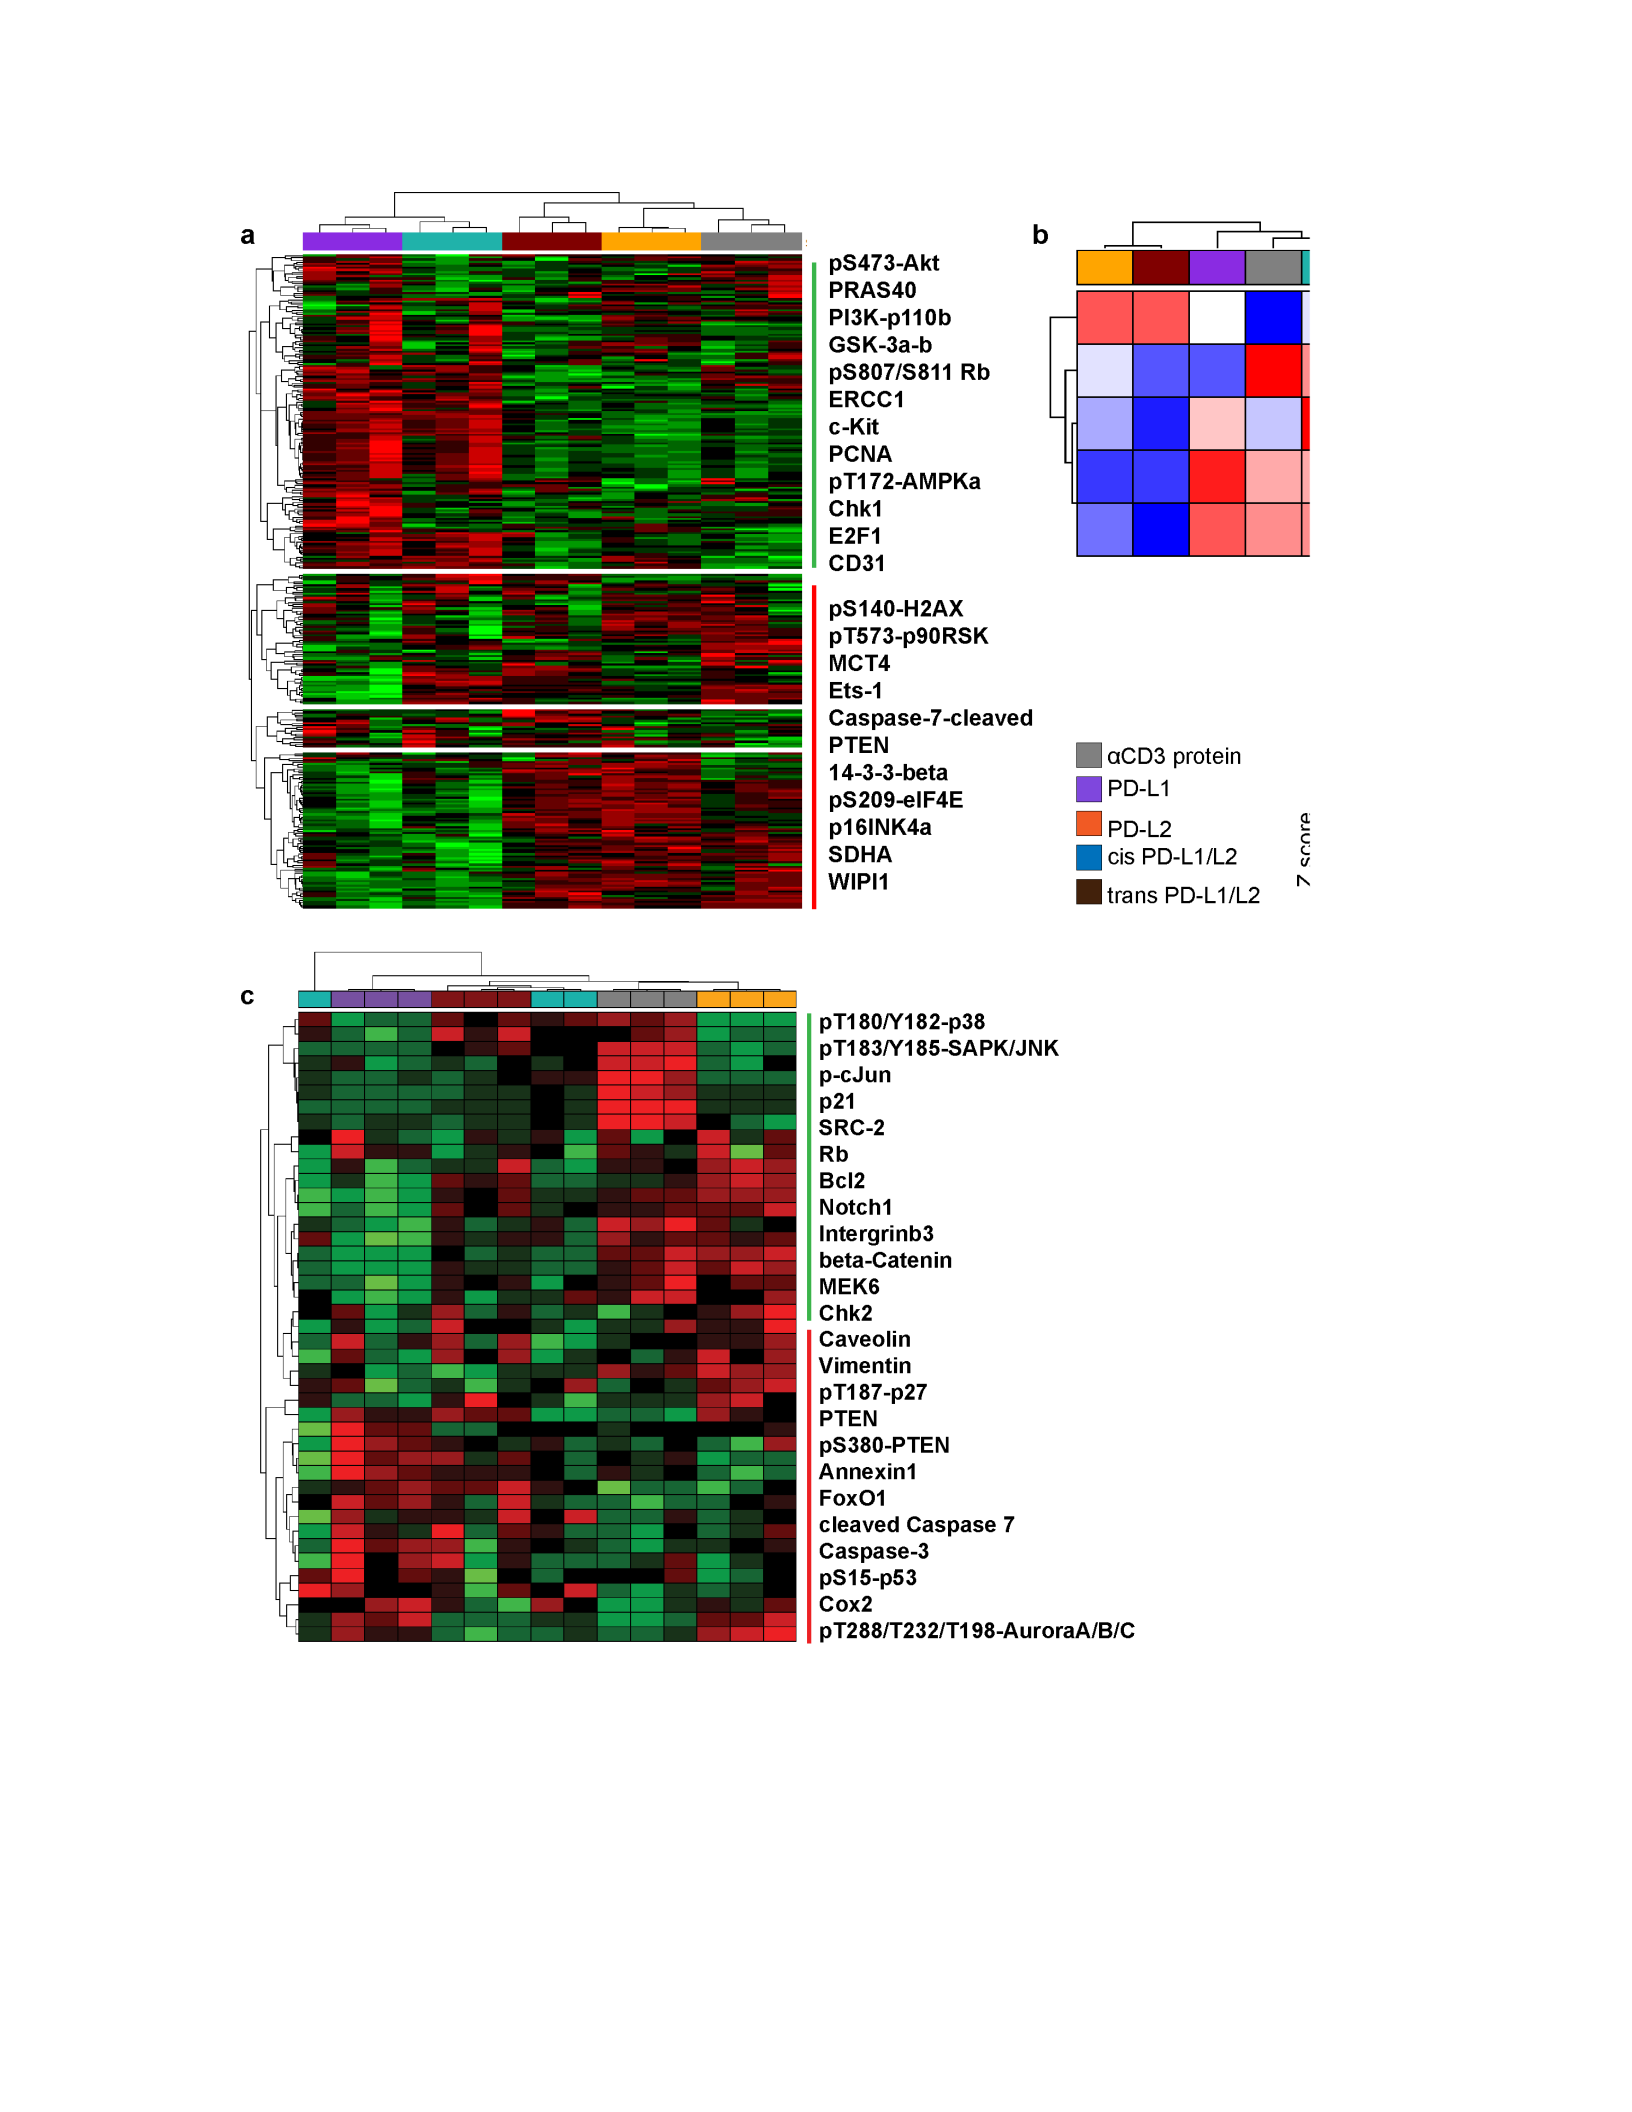
provided a simultaneous signal through PD-1. Hierarchical cluster analysis of normalized
RPPA data from MD Anderson revealed dramatic global differences in the proteomic
signatures of Jurkat T cells exposed to each of the PD-ligands (Figure 4a). Despite binding
to the same co-receptor, Jurkats inhibited by PD-L2 clustered closer to uninhibited Jurkats
and did not resemble the PD-L1 induced signaling repertoire. These observations were also
reproduced in an independent RPPA experiment performed at Baylor College of Medicine that
further highlighted the robustness of our findings (Figure 4c).
At a more granular level we studied the differential protein expression between PD-1/PD-L1
and PD-1/PD-L2 interactions. We observed that phosphor-Akt(S473), PRAS40, p110b-PI3K
were preferentially downregulated while PTEN was upregulated by PD-L2 (Supplemental
Figure S3a), suggesting that PD-1 engagement of PD-L2 and not PD-L1 suppressed the
TCR-CD3 mediated activation of the PI3K/Akt pathway in Jurkat T cells. Similar results were
also observed in the Baylor data (Figure 4a, 4c). As we analyzed the RPPA data further we
found that PD-L2 induced the expression of pro-apoptotic proteins like cleaved Caspase-3,
cleaved Caspase-7 and Annexin that aligned with our earlier observation of enriched
apoptosis in the transcriptomic data.
We also characterized the functional association between the differentially regulated proteins
through literature-driven pathway analysis. We focused on five cellular pathways, namely,
PI3K/Akt, mTOR, Apoptosis, Cell Cycle and Ras/MAPK and calculated pathway activity score
based on protein predictors curated from the literature (Supplemental Figure S3b). In the

40
heatmap, blue color represented a suppressed pathway and red indicated an activated
signature (Figure 4b). Jurkat T cells that received only the TCR-CD3 stimulus showed active
PI3K/Akt, Ras/MAPK, Cell cycle pathways along with an inactive Apoptosis pathway. In
addition to the differential clustering evident in the dendrogram, we also observed an inverse
relationship in the regulation of the assessed cellular pathways between PD-L1 and PD-L2.
We found that PD-L2 inactivated mTOR, PI3K/Akt, Cell cycle and Ras/MAPK pathways at the
proteomic level more potently than PD-L1. This was in contrast to our transcriptomic data
where we concluded that PD-L2 was the weaker inhibitory ligand than PD-L1. Similar to our
transcriptomic data we found the apoptosis pathway to be enriched by the PD-1/PD-L2
interaction. The only point of commonality between PD-L1 and PD-L2 inhibited T cells was
the suppression of the Ras/MAPK pathway by both the PD-ligands. It was surprising to find
that PD-1/PD-L1 did not strongly suppress the PI3K/Akt/mTOR pathway. It is important to
remember that in our experimental set up Jurkat T cells received only a TCR-CD3 activation
in the absence of any co-stimulation. While it is known that CD28 is the primary target for PD-
1/PD-L1 inhibition, our RPPA results suggest that PD-1/PD-L2 inhibition may be more
effective in attenuating the signaling partners downstream to the TCR-CD3 axis. We were
also the first to observe a direct association of PD-L2 and activation of apoptosis in Jurkat T
cells, an impact that was not evident in the PD-L1 sample.
We began our investigation without assuming a redundant role of PD-L2 in T cell function and
reported that PD-L2 binds to PD-1 to induce a distinct inhibitory signaling repertoire that is
supported by transcriptomic and proteomic evidence.
41

42
Figure 4: Characterization of the signaling repertoire induced in Jurkat T cells by PD-
1/PD-L1 and PD-1/PD-L2 at the proteomic level. (a) Hierarchical cluster analysis of RPPA
data of Jurkat T cells inhibited by the indicated PD-ligands expressed on CHO cells. This
experiment was performed at the University of Texas MD Anderson Cancer Center
Proteomics Facility (n= 3 technical replicates). Some proteins that were differentially regulated
by PD-L1 and PD-L2 are indicated (red: upregulated; green: downregulated). (b) Heatmaps
demonstrating mean pathway scores after unsupervised hierarchical clustering. (c)
Hierarchical cluster analysis of differentially enriched proteins from the RPPA data performed
at the Baylor College of Medicine (p value cutoff <=0.05).

43
3.5. PD-L2 engages PD-1 to weakly suppress TCR-CD3 activation and induce apoptosis
in Jurkat T cells.
While both our microarray and RPPA showed enrichment of apoptosis by PD-L2, the
regulation of other pathways associated with T cell activation were incongruent between the
two experiments. The microarray results showed that PD-L1 was a more potent inhibitory
ligand and suppressed pivotal pathways like mTORC1 and TNFα signaling via NFKB.
However, from our RPPA experiment we observed that PD-L2 was better at suppressing TCR-
CD3 activation. Nevertheless, both the platforms helped prove our hypothesis that the
inhibitory signaling induced through PD-1 by PD-L1 and PD-L2 is distinct.
It was imperative that we validated our results in functional assays. We continued with the
same experimental set-up of CHO cells overexpressing PD-ligands and Jurkat T cells
expressing PD-1. We also decided to analyze the temporal kinetics of PD-L1 and PD-L2
mediated inhibition and performed co-culture assays over the course of 24, 48 and 72 hours.
We first tested our earlier observation of upregulation of apoptosis by PD-1/PD-L2 interaction.
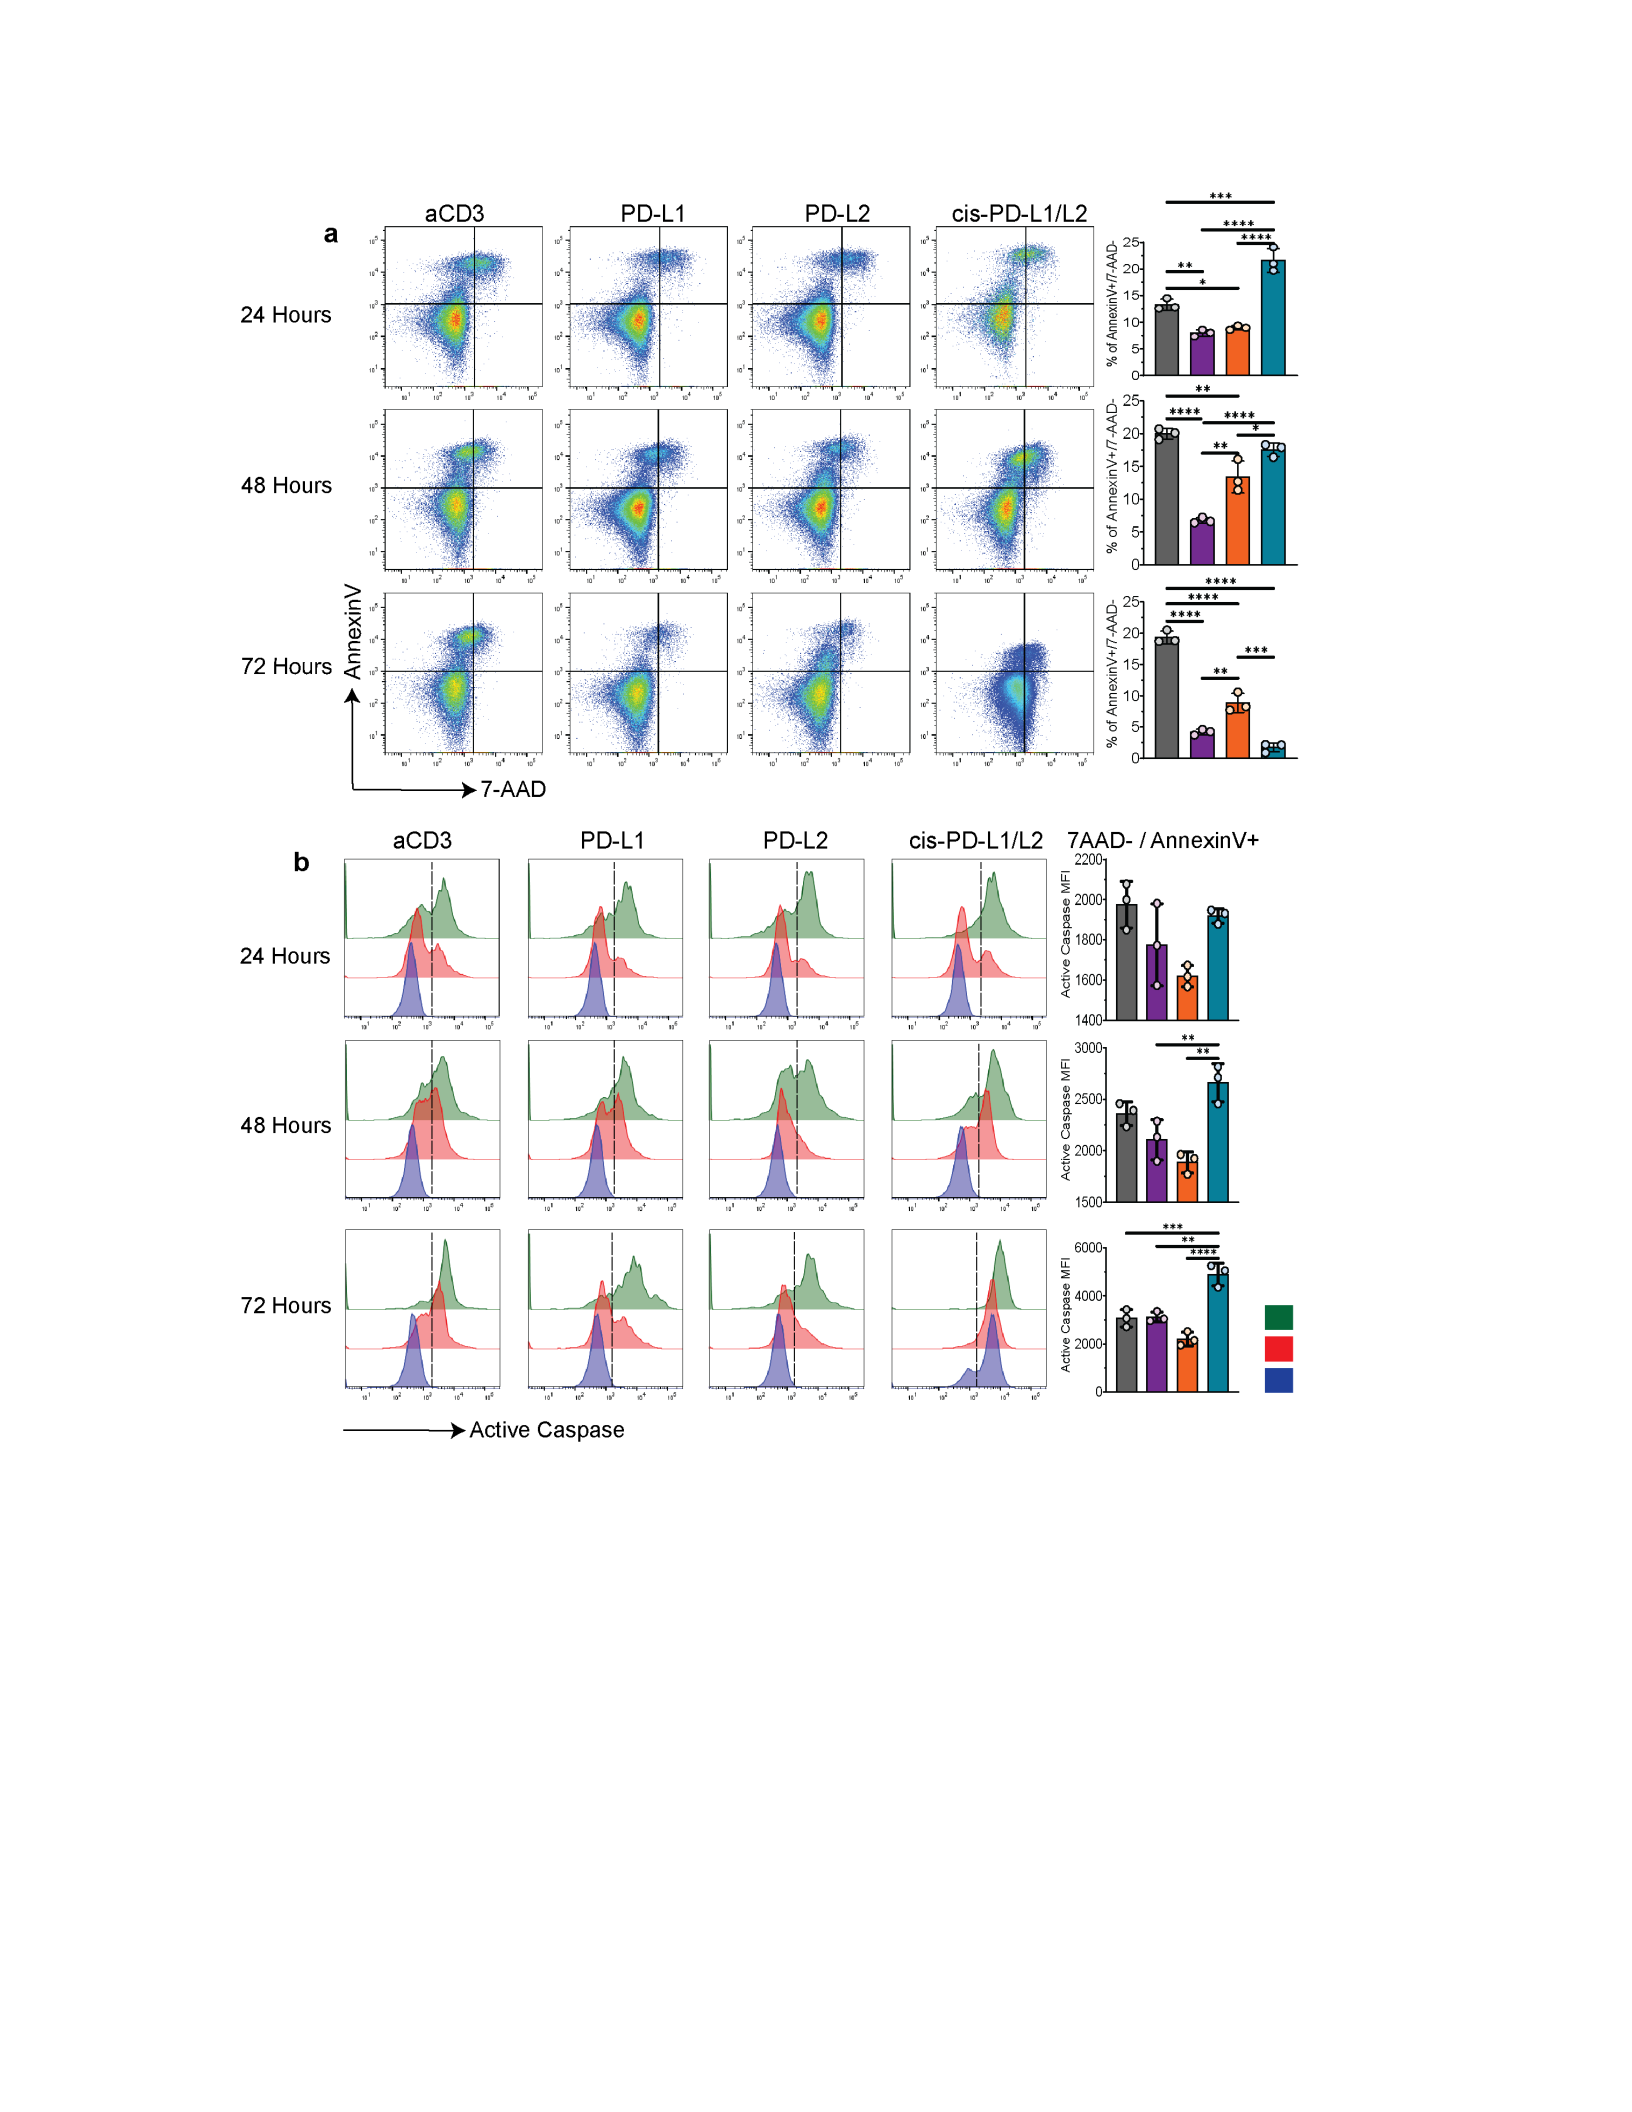
Apoptosis of Jurkat T cells was determined by staining with AnnexinV and 7-AAD (Figure 5a).
We also quantified active caspases using Z-VAD-FMK, a caspase inhibitor conjugated to FITC
for detection by flow cytometry (Figure 5b). The caspase inhibitor is a cell permeable
molecule that irreversibly binds to active caspases in Jurkat T cells. We gated PD-1+ Jurkat
T cells to exclude any possible CHO cell contamination and analyzed AnnexinV/7-AAD
staining by flow cytometry. Early apoptosis was characterized as AnnexinV+/7-AAD-, late
apoptosis as AnnexinV+/7-AAD+ and live cells as AnnexinV-/7-AAD- in the FACS dot plots.
The Jurkat T cells that were only activated through the TCR-CD3 axis and not exposed to any
ligands remained consistent with 20% of PD-1+ cells in early apoptosis. Jurkat T cells
stimulated via TCR-CD3 are susceptible to induction of apoptosis. After 24 hours of co-culture,
we did not observe any significant differences in the viability of Jurkats across the different

44
groups and noticed that CHO-cis-PD-L1/L2 induced a 2-fold increase in apoptosis over the
mono expressing CHO cells, CHO-PDL1 and CHO-PDL2. The differential regulation of
apoptosis between PD-L1 and PD-L2 became evident after 48 hours when we saw that PD-
L2 inhibited Jurkats had a significantly higher percentage of cells in early apoptosis than PD-
L1 inhibited Jurkats despite comparable viability across the two samples. At 72 hours, PD-L2
experienced Jurkats still retained a higher percentage of early apoptotic cells however the
degree of difference between PD-L1 and PD-L2 was reduced. The initial induction of
apoptosis by CHO-cisPD-L1/L2 cells contributed to the dramatic drop in viability to 30% at the
end of the experiment. In addition to AnnexinV staining we also evaluated the activation of
caspases in Jurkat T cells inhibited by PD-ligands. Even though we recorded statistically
significant differences between PD-L1 and PD-L2 in AnnexinV staining, we found that the
levels of activated caspases in Jurkats exposed to PD-L1 or PD-L2 were comparable
suggesting that caspase-independent mechanism of apoptosis may be at play in our
experiment. It was also interesting to find viable Jurkat cells cocultured with CHO-cis-PD-
L1/L2 that were positive for active caspases indicating towards possible non-apoptotic role of
caspases.
Taken together we observed that apoptosis in Jurkat T cells was a consequence of TCR-CD3
activation that was sub-optimally mitigated by PD-L2 due to a weaker inhibitory signal via PD-
1. The preferential induction of apoptosis in Jurkat T cells by CHO-cis-PDL1/L2 may have
relevance in the context of co-expression of the PD-1 ligands in human diseases like cancer.
45
Figure 5: PD-1/PD-L2 complex mediates a weaker inhibitory signal than PD-1/PD-L1 that
sub-optimally suppresses activation induced apoptosis in Jurkat T cells. (a) Jurkat T
cells were co-cultured with CHO cells overexpressing the indicated ligands for 72 hours and
the percentage of apoptosis was measured by flow cytometry through AnnexinV and 7-AAD
staining. Bar plots depict the percentage of early apoptosis cells (7AAD-AnnexinV+) and live
cells (7AAD-) in each sample. (b) We also measured the levels of active caspase by using the
CaspGLOW Fluorescein Active Caspase Staining kit. The mean fluorescence intensity of
activate caspases in early apoptotic cells across the tested samples is depicted. Statistical
significance was calculated using a one-way ANOVA. *p< 0.05, **p<0.01, ***p<0.001,
****p<0.0001.

46
3.6. PD-L2 engages PD-1 to inhibit TCR-CD3 activation of primary human T cells
through a mechanism that is distinct from PD-L1
Our work so far leveraged Jurkat T cells as the model system to elucidate signaling
mechanisms associated with the PD-1/PD-L1/PD-L2 signaling axis. While the system
facilitated our high-throughput molecular studies we also acknowledged the short-comings of
a transformed T-cell line and validated our results in primary human T cells. We utilized
PBMC-isolated human T cells to confirm the differential inhibitory signal mediated by PD-L1
and PD-L2 via PD-1. Since naïve T cells do not express PD-1 on the surface we activated
PBMC-isolated human T cells with aCD3/aCD28 coated beads for 40 hours and cocultured
the activated T cells with CHO cells expressing PD-ligands for 24 hours. After coculture we
flash froze whole cell pellets for RPPA analysis. Additionally, we also utilized the same
experimental setup and stained the T cells with Propidium Iodide (PI) and AnnexinV/7-AAD to
evaluate the impact of PD-ligands on cell cycle and apoptosis.
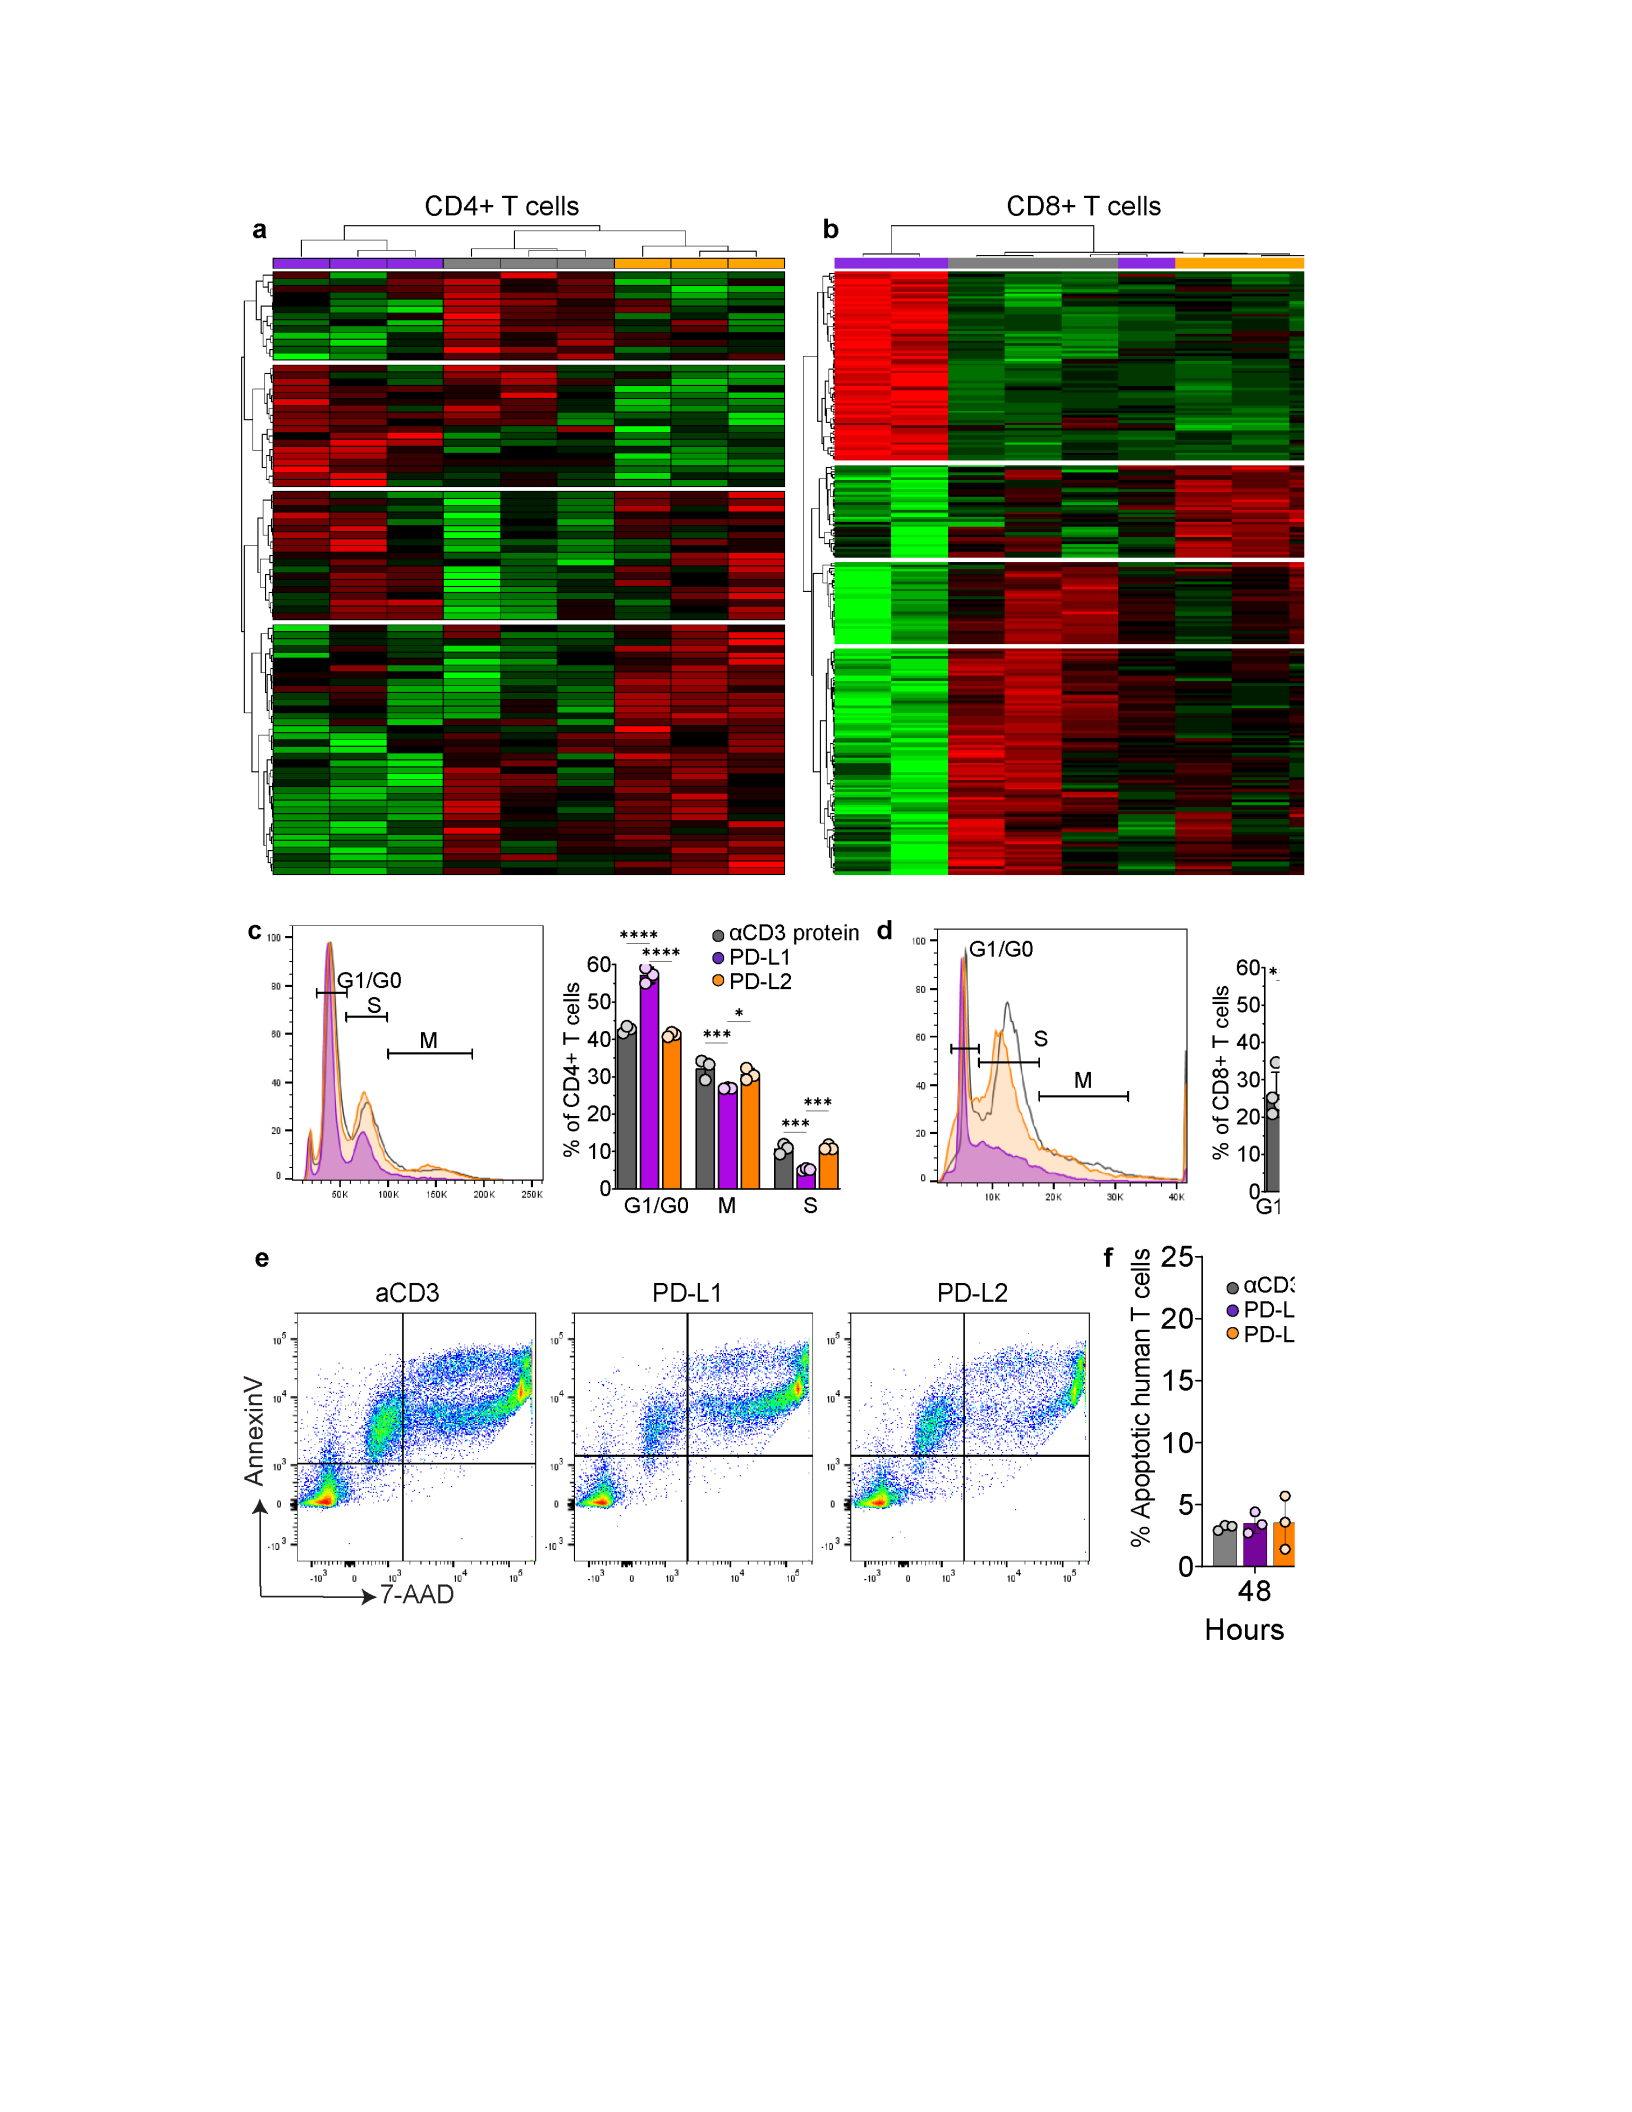
The differential protein repertoire elicited by PD-L1 and PD-L2 in Jurkat T cells was replicated
in CD4+ and CD8+ human T cells as well (Figure 6a, 6b). Hierarchical clustering of the RPPA
results emphasized the distinct protein signaling patterns and confirmed that PD-L2 inhibited
human T cells clustered away from PD-L1 inhibited T cells and resembled more closely to
TCR-CD3 activated human T cells.
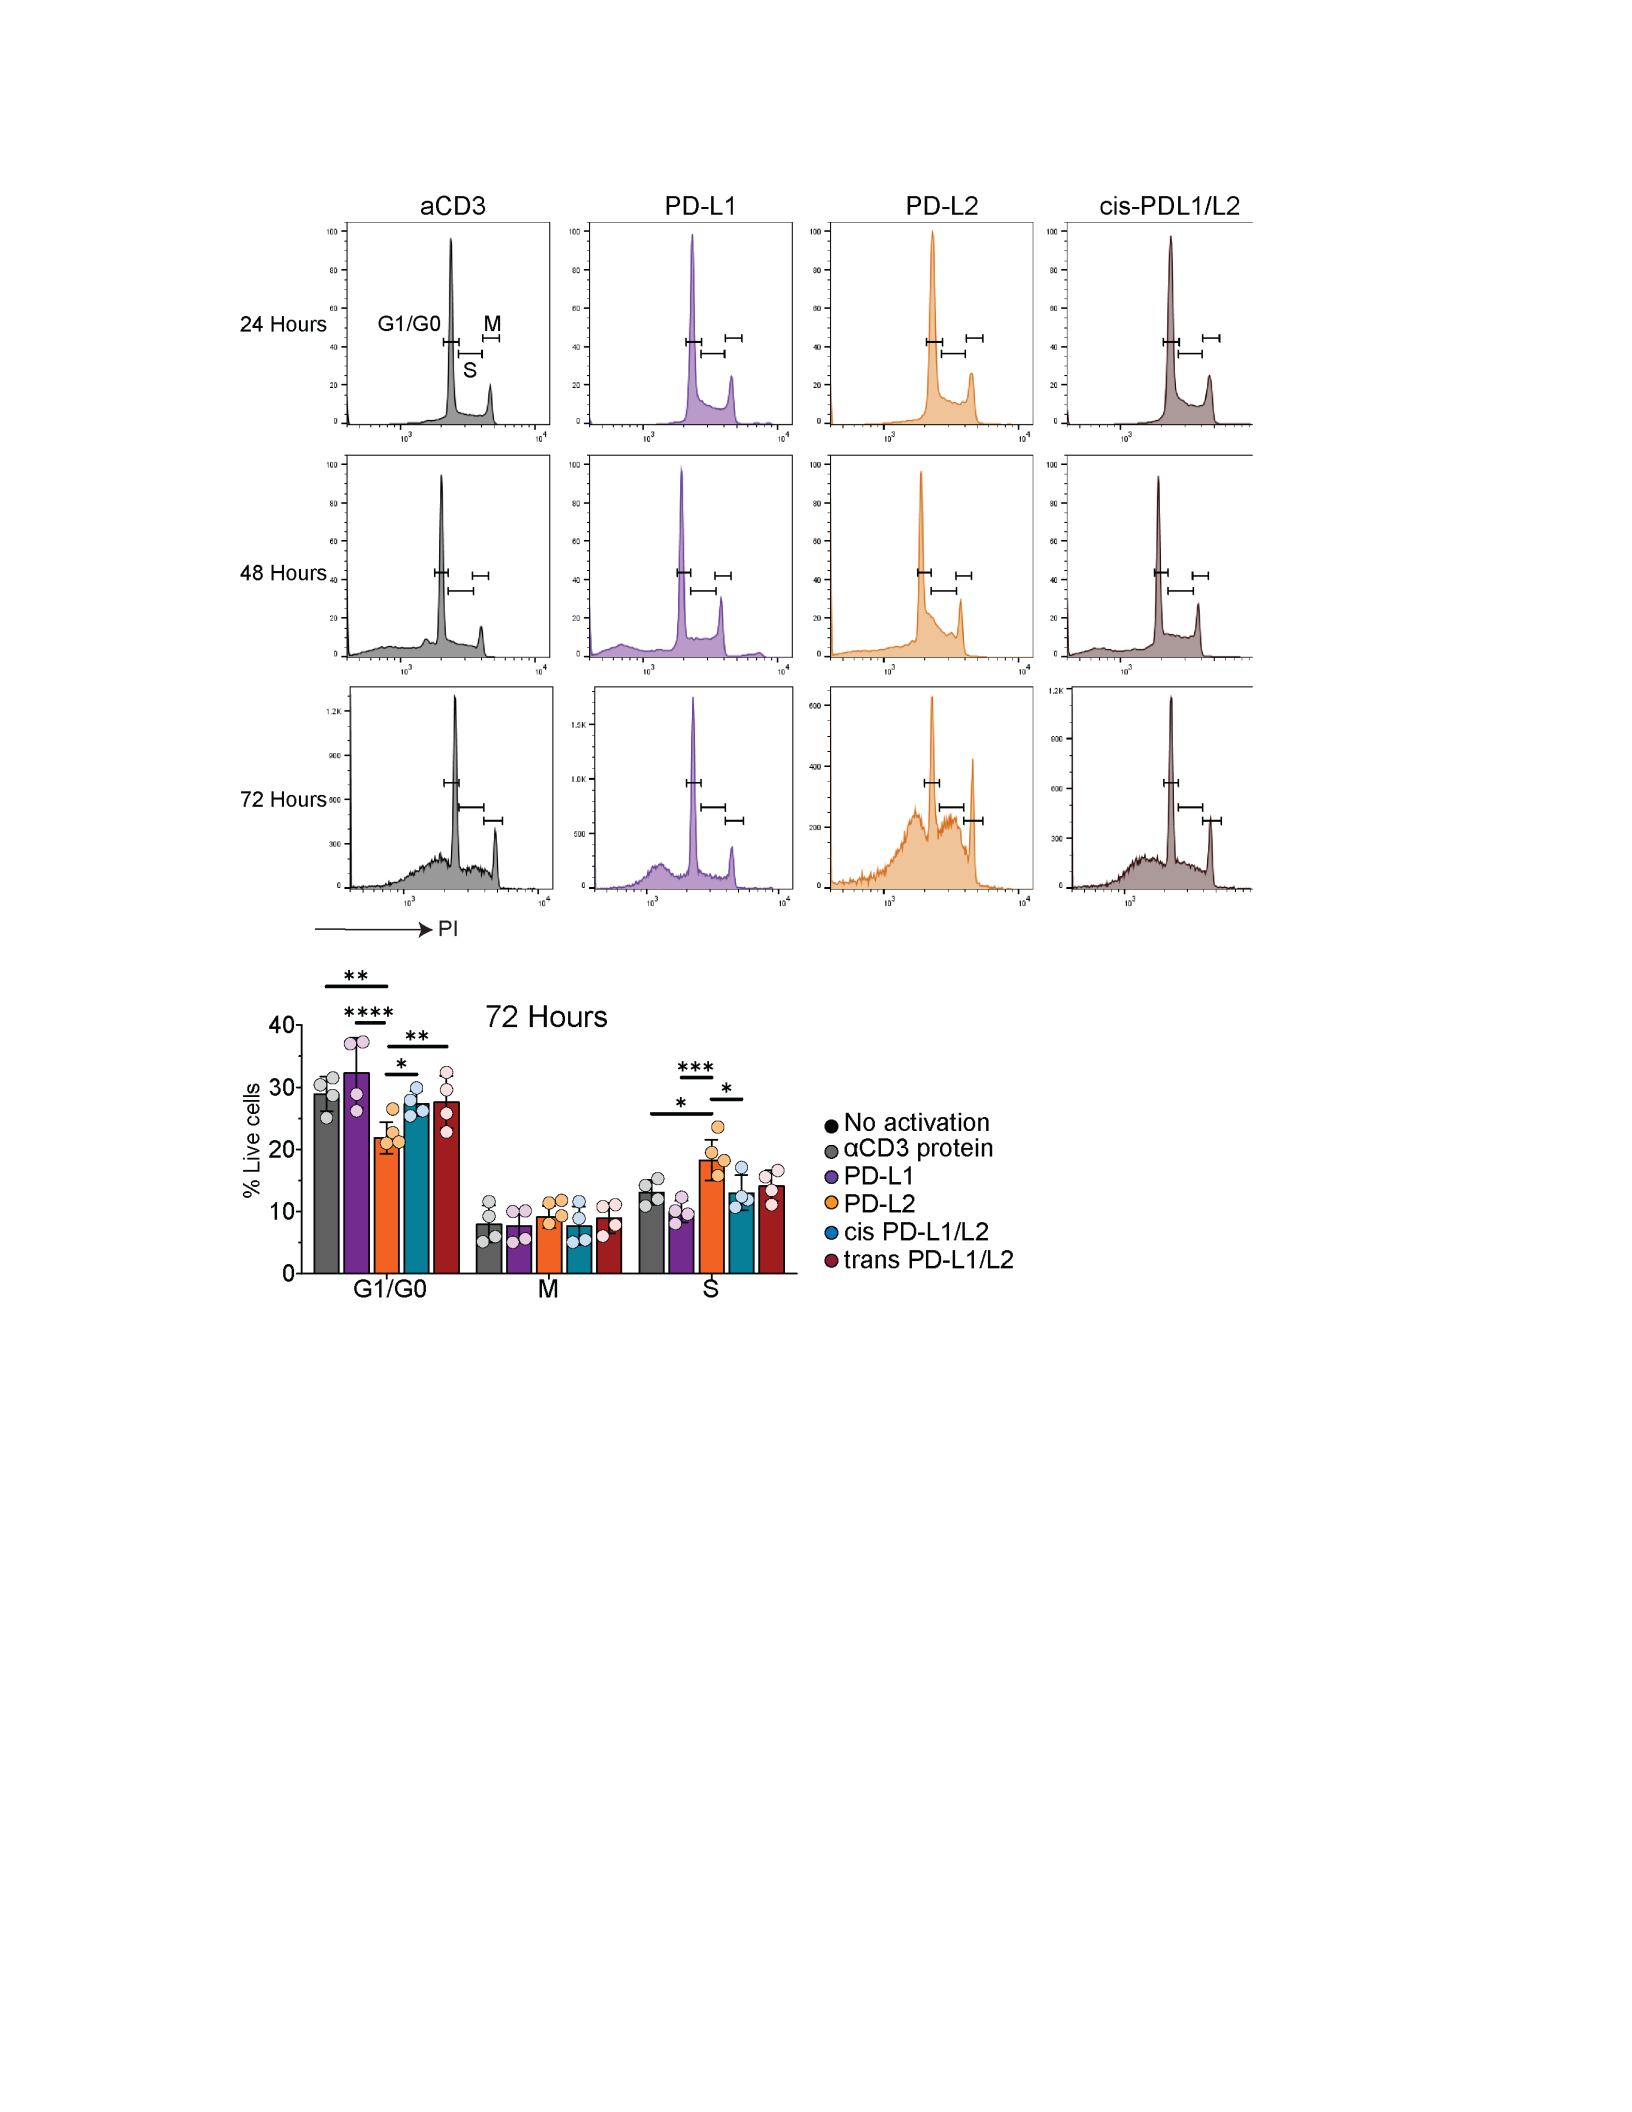
When we tested the influence of PD-L1 and PD-L2 on the cell cycle of Jurkat T cells we found
that PD-L2 preferentially accumulated Jurkat T cells in the S phase depicted by Propidium
iodide (PI) staining (Supplemental Figure S6). We chose to corroborate our previous findings
in functional assays using PBMC-isolated human T cells. Since we observed a 2-fold increase
in the % of Jurkat T cells in the S-phase (Supplemental Fig S4), we speculated that PD-L2
unlike PD-L1 did not arrest T cells in the G1/G0 phase rather accumulated T cells in the S
phase. This was also in line with our GSEA findings where we found PDL2 downregulated

47
pathways like Mitotic Spindle Pathway that contribute to the execution of the S phase in the
cell cycle. When we investigated the impact of PD-ligands on the cell cycle of primary human
T cells we found that PD-L1 restricted T cells in the G1/G0 but PD-L2 did not impede the
progression of the cell cycle and was comparable to activated T cells (Figure 6c, 6d). We
also studied the correlation between PD-L2 and apoptosis in primary human T cells and found
that only after 96 hours of coculture with PD-ligands did we observe a significant difference in
the percentage of apoptotic human T cells (Figure 6e, 6f). Once again, the effect of PD-L2
on human T cells was comparable to that of activated T cells. We conclude that PD-L2 sends
a weaker inhibitory signal through PD-1 which in turn contributes to a downstream signaling
mechanism that was distinct from PD-L1.
48

49
Figure 6: PD-L2 binds to PD-1 to induce a signaling repertoire that is distinct from PD-
L1 in CD4+ and CD8+ PBMC-isolated T cells. (a) (b) Hierarchical cluster analysis of RPPA
data of human PBMC-isolated CD4+ and CD8+ T cells co-cultured with CHO cells expressing
the indicated PD-Ligands. (c)(d) Percentage of CD4+ and CD8+ T cells in different stages of
the cell cycle based on propidium iodide staining after 72 hours of co-culture with PD-ligands.
(e)(f) Percentage of early apoptotic CD3+ T cells that are AnnexinV+7-AAD- after co-culture
for indicated time durations with CHO cells overexpressing PD-L1 or PD-L2. Statistical
significance was calculated using a one-way ANOVA. *p< 0.05, **p<0.01, ***p<0.001,
****p<0.0001.
50
Supplemental Figure S4: PD-L2 engagement of PD-1 arrests the Jurkat T cells in the S
phase of the cell cycle. (a)Jurkat T cells were co-cultured with CHO cells expressing PD-L1,
PD-L2 or co-express PD-L1 and PD-L2 for the indicated time durations and stained with
propidium iodide to quantify the percentage of live cells in different stages of the cell cycle.
Statistical significance was calculated using a one-way ANOVA. *p< 0.05, **p<0.01,
***p<0.001, ****p<0.0001.

51
3.7. PD-L1 and PD-L2 rely on the ITSM region in PD-1 cytoplasmic tail to repress TCR-
CD3 activation of Jurkat T cells
To further elucidate the differential capacity of PD-L1 and PD-L2 to inhibit T cell activation, we
evaluated the inhibitory effect on membrane proximal TCR signaling partners. We lysed Jurkat
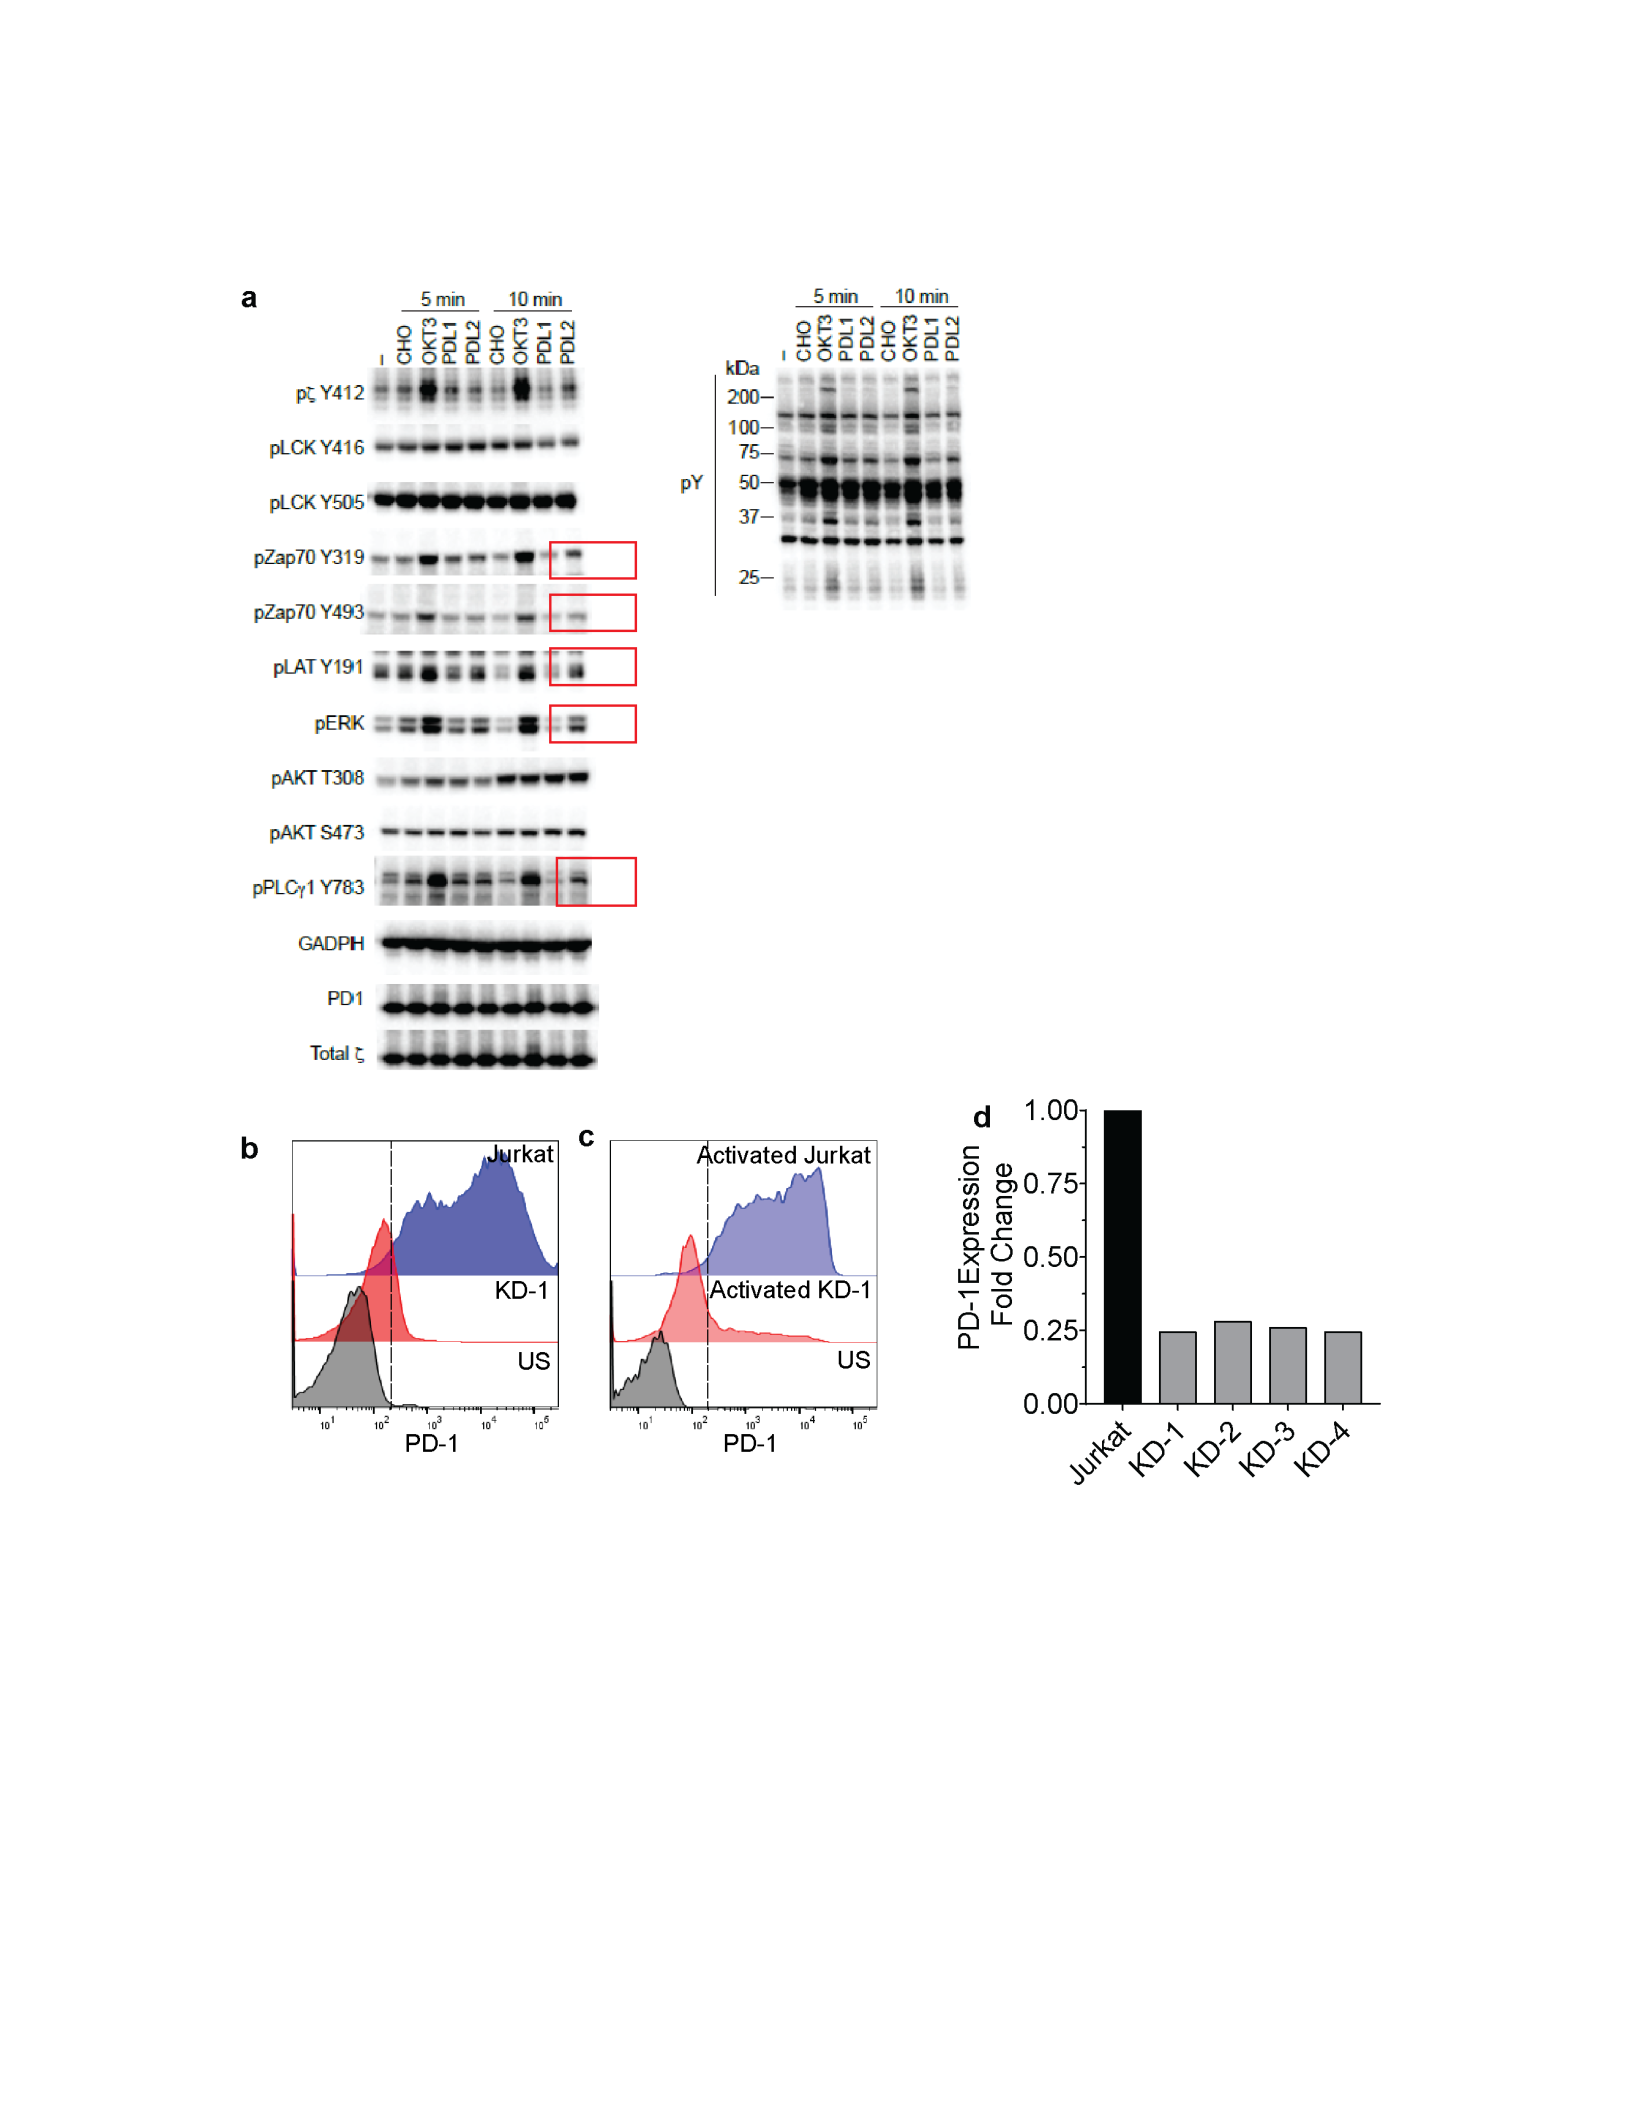
T cells after exposure to PD-ligands (5 mins or 10 mins) and blotted with antibodies against
phospho-epitopes of proteins in the TCR-CD3 signaling axis. We observed that PD-L2 was a
weaker inhibitor than PD-L2 since at 10 mins PD-L1 more potently dephosphorylated proteins
like ZAP70, LAT, ERK and PLCʏ (Figure 7a). However, PD-L2 was still inhibitory relative to
no PD-ligand available for PD-1 engagement.
Several years of research focused on PD-1 contributed towards our current understanding
that the ITSM region in the cytoplasmic tail of PD-1 recruits SHP-2, a phosphatase that is
responsible to dephosphorylate elements of the CD28 and TCR-CD3 signaling axis[67].
However, these studies were largely based on PD-1 engagement of PD-L1 and did not look
into the relevance of PD-L2 in this model. Based on our findings we hypothesized that PD-L2
utilizes the ITIM region in the cytoplasmic tail of PD-1 instead of the ITSM to mediate the
weaker inhibitory signal via PD-1. We performed CRISPR-Cas9 guided knock-down of the
surface expression of endogenous PD-1 in the NFAT-luc reporter Jurkat T cells and confirmed
the levels of PD-1 expression by flow cytometry (Figure 7b) and quantitative-PCR (qPCR)
(Figure 7d). We confirmed the absence of PD-1 expression on Jurkat T cells even after
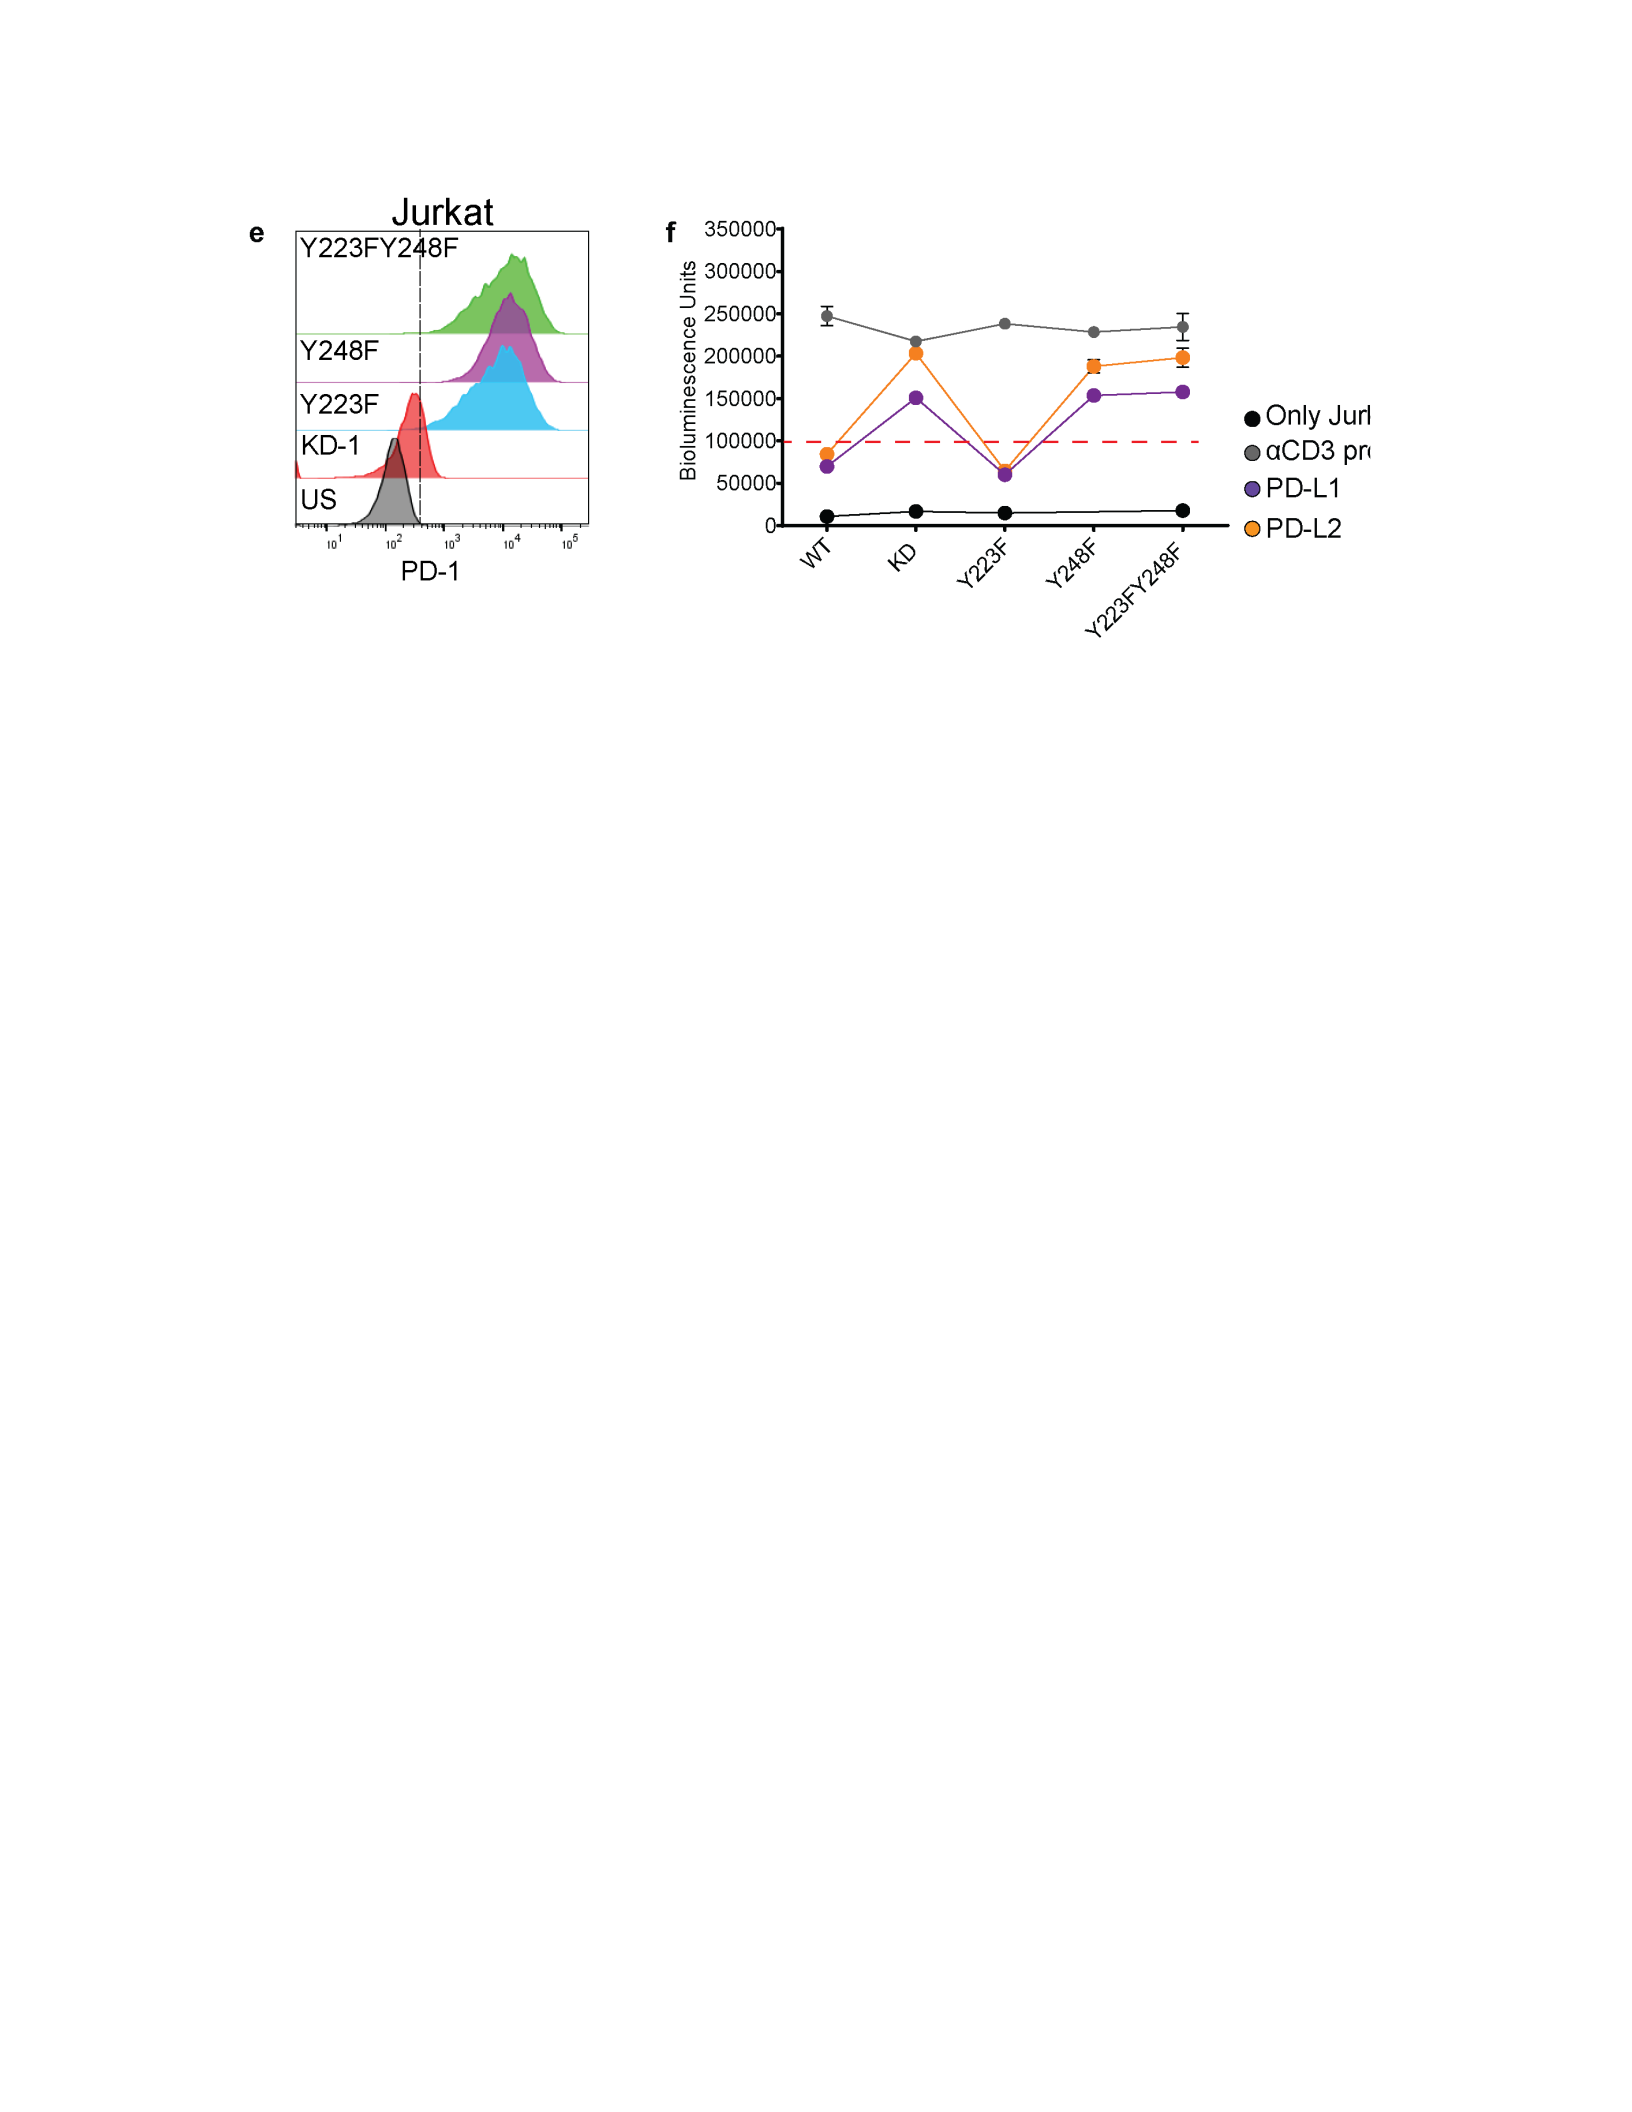
activation with aCD3/aCD28 dynabeads (Figure 7c). We then transduced the PD-1KD Jurkat
T cells with a phosphor-dead ITIM mutant (Y223F), or a phosho-dead ITSM mutant (Y248F)
or a double mutant with inactive ITIM and ITSM regions (Figure 7e). A phospho-dead mutant
will not be able to create a docking site for any relevant phosphatases even if the extracellular
domain of PD-1 engages a cognate ligand. Similar to our previous experiment in Fig 1, TCR-
CD3 activation is quantified as a measure of bioluminescence. WT Jurkats express PD-1 on

52
the surface that retain the endogenous cytoplasmic domains and exhibit reduced
bioluminescence due to inhibition by PD-L1 or PD-L2 (Figure 7f). The bioluminescence was
restored by Jurkat T cells wherein PD-1 surface expression was knocked down. Y223F(ITIM)
PD-1 mutant had an intact ITSM region that continued to inhibit T cell activation but the
Y248F(ITSM) PD-1 mutant showed increased bioluminescence suggesting that the ITSM
region is indispensable for PD-1 mediated inhibition of NFAT-activation in T cells. Therefore,
our hypothesis was disproved since both the ligands relied on the ITSM region to transmit the
inhibitory signal downstream of the transmembrane PD-1 co-receptor.
53
54
Figure 7: The ITSM region on the cytoplasmic tail of PD-1 is indispensable for PD-1/PD-
L2 mediated inhibition TCR-CD3 activation in Jurkat T cells. (a) Jurkat T cells expressing
PD-1 on the surface were co-cultured with PD-L1 and PD-L2 for 5 and 10 minutes and blotted
for phosphor-proteins associated with the TCR-CD3 signaling axis. (b) Quantification of PD-1
expression in Jurkat T cells transiently transfected with Cas9-gRNA vector specific to PD-1
by flow cytometry, after activation with aCD3/CD28 dynabeads (c) and qPCR (d). (e) KD-1
Jurkats were retrovirally transduced with indicated mutant forms of PD-1 and sorted based on
restored PD-1 expression. (f) 4X10⁴ CHO cells overexpressing indicated proteins and 5X10⁴
mutant forms of PD-1+ Jurkat T cells (NFAT-RE-Luciferase reporter) were co-cultured for 6
hours and TCR-CD3 activation was measured by luciferase assay according to
manufacturer’s instructions and represented as bioluminescence units. Statistical significance
was calculated using a one-way ANOVA. *p< 0.05, **p<0.01, ***p<0.001, ****p<0.0001.

55
3.8. PD-1/PD-L2 inhibited T cells are poised to functionally recover more readily than
PD-1/PD-L1 inhibited T cells.
Our findings so far discovered and detailed the distinct inhibitory signal mediated by PD-L2
through PD-1 in humans. PD-L2 binds to PD-1 to transduce a weaker inhibitory signal than
PD-L1 resulting in a distinct signaling repertoire downstream to PD-1. We hypothesized that
PD-L2 mediated inhibition of T cells through PD-1 leaves T cells in a less inhibited state than
PD-L1 and allows the inhibited T cells to recover more readily. We tested this hypothesis by
inhibiting pre activated human T cells (to induce expression of PD-1) from 2 different donors
with CHO-hPDL1 and CHO-hPDL2 for 72 hours and then rested them overnight before re-
activating them with CD3/CD28 T cell activator beads for another 72 hours and analyzed the
levels of cytokines in the supernatant by cytokine bead array (Figure 8a). Post inhibition we
detected low levels of cytokines in the supernatant and no difference was observed across
the samples. The absence of co-stimulatory signal for 72 hours during inhibition must have
resulted in the low levels of cytokine produced by the uninhibited T cells (Figure 8a). Post
recovery only PD-L2 inhibited T cells produced IL2 and TNFα significantly more than PD-L1
inhibited T cell and was comparable to the uninhibited T cells (grey) (Figure 8c). This data
supports our hypothesis that PD-L2 inhibited T cells recovered more effectively than PD-L1
inhibited T cells and readily produced effector cytokines like IL-2 and TNFα. In future
investigations it will be important to expand our hypothesis to other effector functions like
cellular cytotoxicity and granzymeB production and titrate the reactivation stimuli to find out
the upper limit of re-activation intensity that propels the PD-L1 inhibited T cells to recover to a
level that is comparable to uninhibited and PD-L2 inhibited T cells.
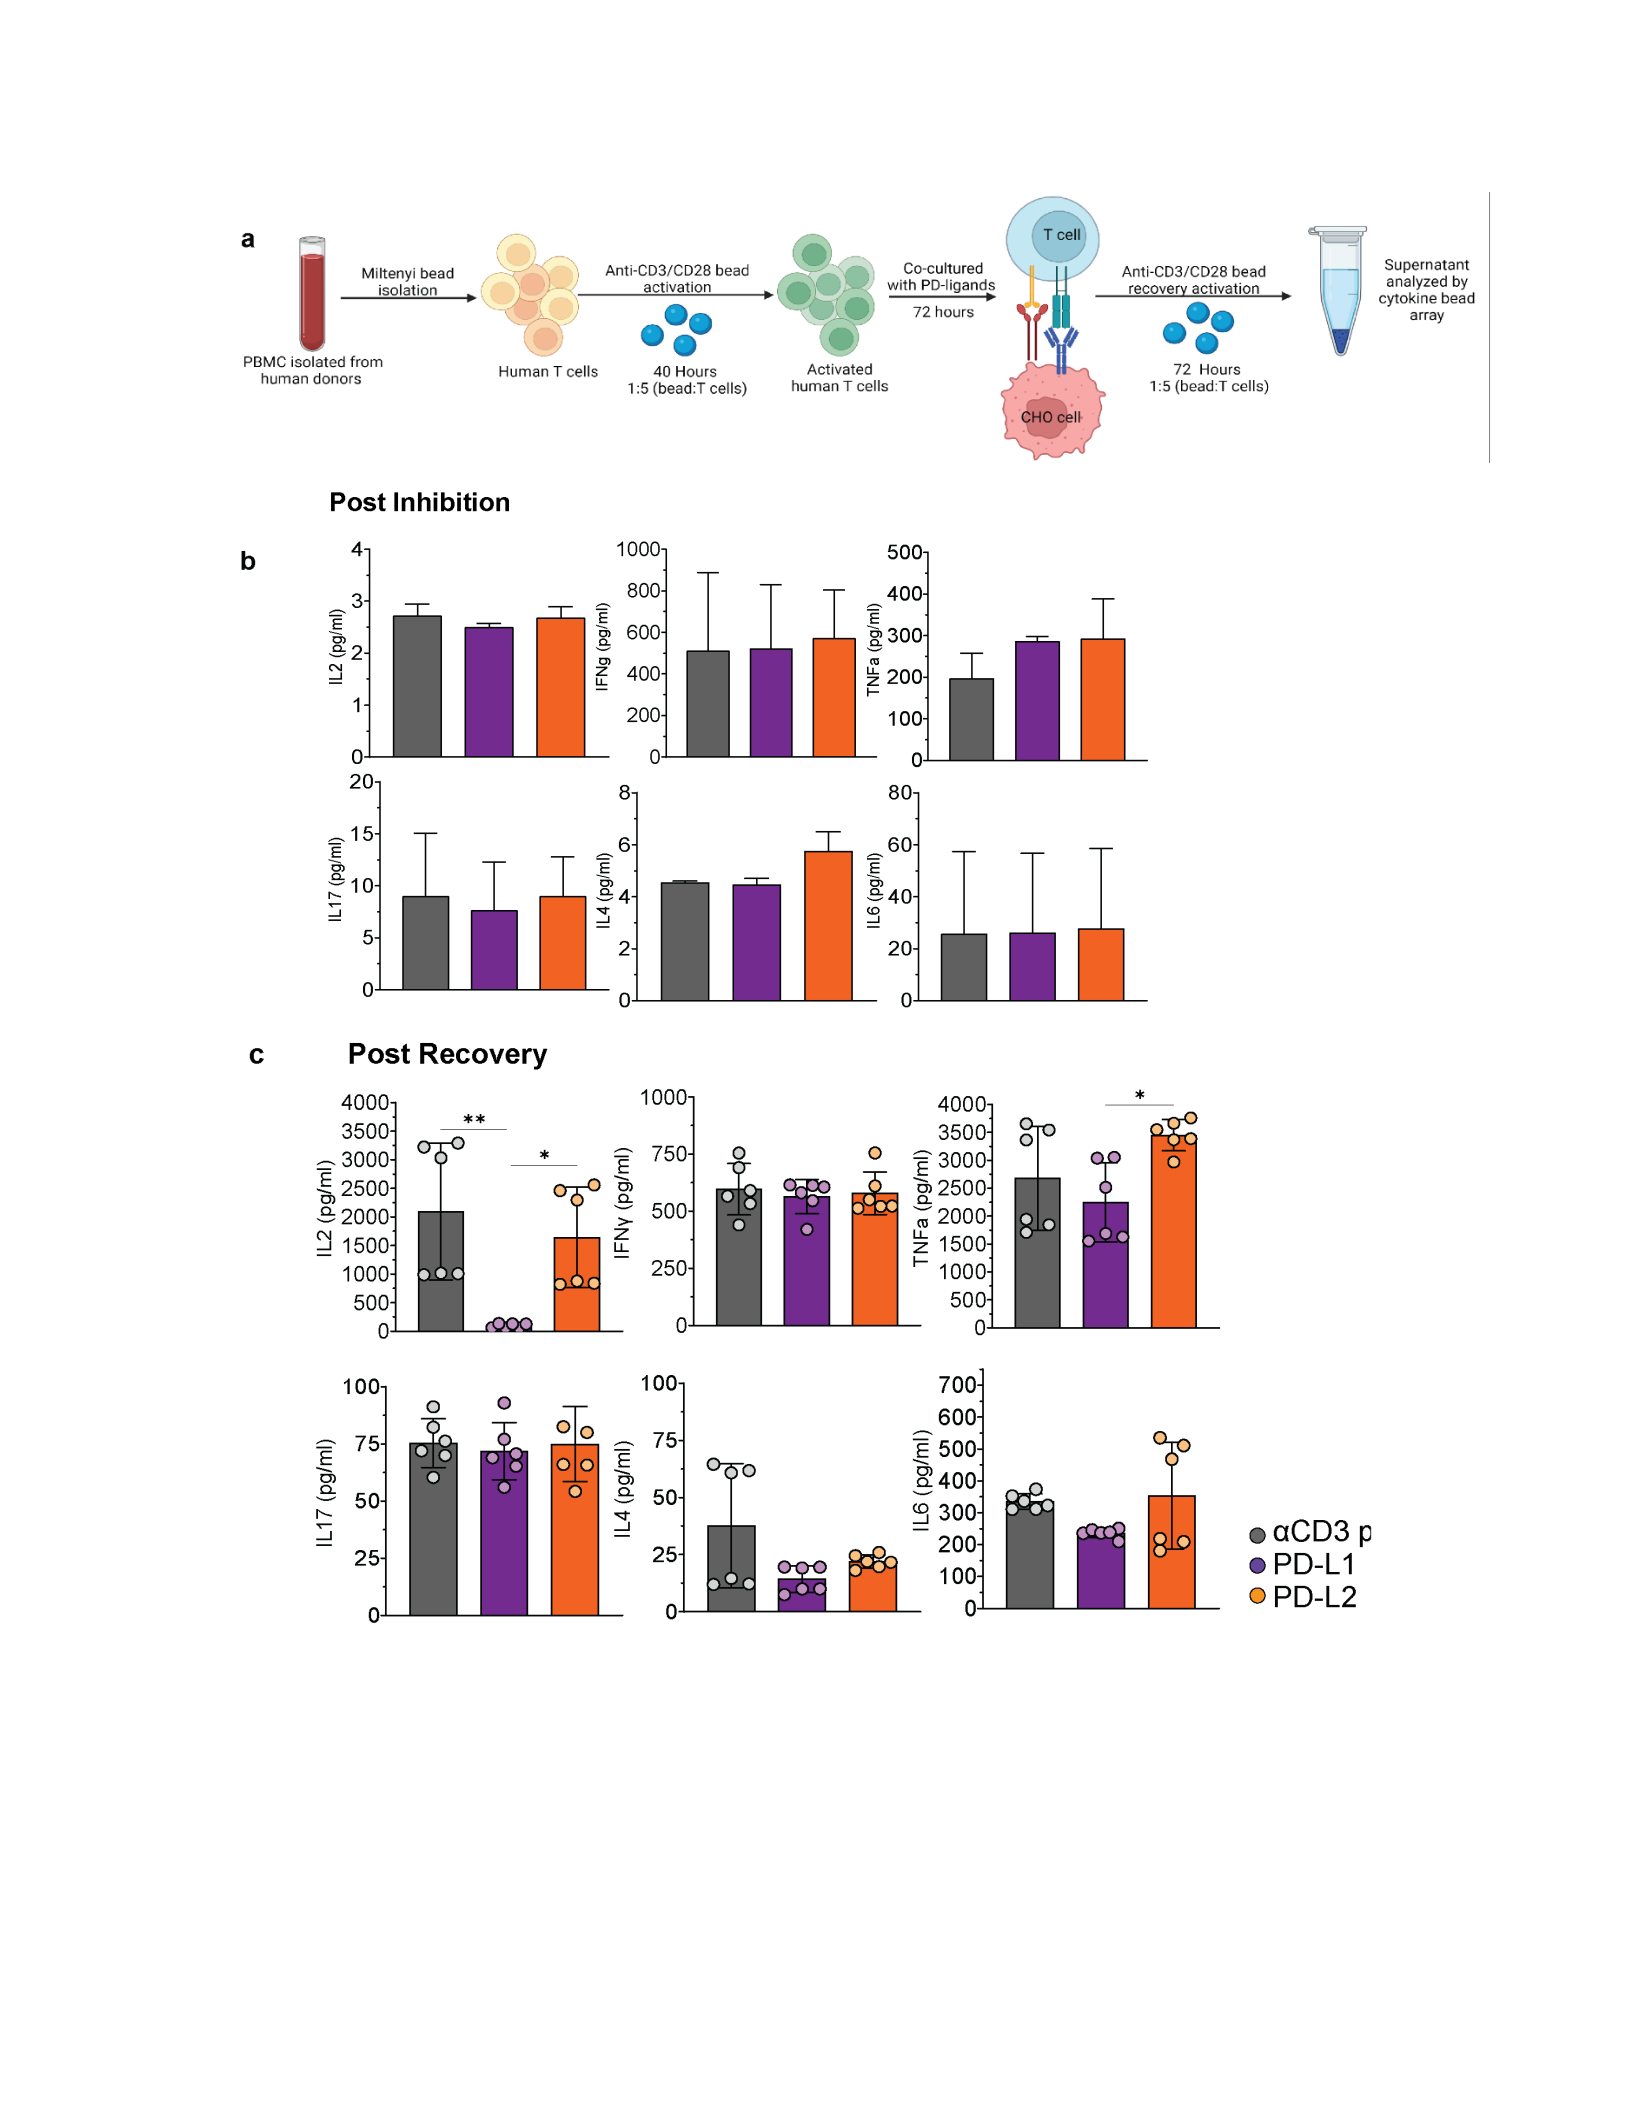
56
Figure 8: PD-L2 inhibition through PD-1 allows T cells to functionally recover more
readily than PD-L1. (a) PD-ligand mediated inhibition and recovery protocol as described in
detail in methods. (b) Evaluation of cytokine levels in the supernatant immediately after the
72 hours co-culture with PD-ligands by cytokine bead array. (c) Evaluation of cytokine levels
by using a cytokine bead array after re-activation of T cells using CD3/CD28 T cell activator
beads. Statistical significance was calculated using a one-way ANOVA. *p< 0.05, **p<0.01,
***p<0.001, ****p<0.0001. N= 2 donors n=3 technical replicates.

57
Chapter 4: Discussion
This dissertation investigated the unique role of PD-L2 in modulating human T cell responses
and discovered the following:
1) Human PD-L2 does not exhibit the T cell co-stimulatory function observed in mice.
2) PD-L2 engages PD-1 to induce a distinct signaling repertoire in human T cells.
3) PD-L2 mediates a weaker inhibitory signal through PD-1 than PD-L1 in human T cells.
4) PD-L2 inhibited T cells are able to functionally recover more readily than PD-L1
inhibited T cells.
As of February 2023, the therapeutic landscape of PD-1/PD-L1 inhibitors consisted of 180+
pharmaceutical companies with 200+ candidates in various stages of drug development[128].
The current arsenal of anti-PD-1/PD-L1 monoclonal antibodies comprises of 7 different drugs
that are FDA-approved for treatment across 24 cancer types[6]. While immune checkpoint
inhibitors revolutionized the field of immuno-oncology it is also important to acknowledge that
innovation and improvement of novel therapeutics against the PD-1 signaling circuit can be
achieved only through a comprehensive understanding of the underlying biology.
Since its discovery in 2001, PD-L2 was assumed to have overlapping immune modulatory
functions with PD-L1 until a second binding partner of PD-L2, repulsive guidance molecule b
(RGMb) was reported in 2014[129]. Thereafter the role of PD-L2 in T cell responses was
controversial because both coinhibitory and costimulatory functions were attributed to the
ligand. Chen et al. showed that a recombinant mutant PD-L2 protein (K113S) that retained its
binding affinity to RGMb but not to PD-1 co-stimulated CD4+ T cell responses to promote Th1
polarization in a murine model for asthma[125]. In parallel, other research groups published
data that denied any dualism in the function of PD-L2 and emphasized PD-L2 as a coinhibitory
ligand to T cell responses[130–132]. Researchers overwhelmingly relied only on PD-L1 as

58
the inducer of PD-1 in their investigations and as a result the therapeutic potential of PD-L2
remained in the shadows of PD-1/PD-L1 blocking agents. The contentious function of PD-L2
may have contributed to the singular focus of the field on PD-L1 as the cognate ligand of PD1.
I began my PhD work with the general hypothesis that the restricted expression pattern of PD-
L2 in normal human physiology and cancer combined with its unique biophysical properties
underscore PD-L2 as an independently important ligand of the PD-1 signaling axis. My
dissertation demonstrated that PD-L2 is a non-redundant ligand of human PD-1 that inhibits
T cell activation through a mechanism that is distinct from PD-L1. We further characterized
the distinct inhibitory signal and found that PD-L2 inhibited T cells showed higher levels of
apoptosis when compared to PD-L1 and demonstrated slower temporal kinetics in the
dephosphorylation of the TCR-CD3 signaling axis. Additionally, we also showed that the PD-
1/PD-L2 interaction unlike PD-1/PD-L1, allowed T cells to progress through the cell cycle and
avoid being arrested in the G1/G0 phase. Our work challenged prior scientific literature that
assumed a redundant function for PD-L2. We were the first to discover that human PD-L2,
despite its higher binding affinity transmitted a weaker inhibitory signal through PD-1, which
in turn allowed the inhibited T cells to functionally recover more readily when re-exposed to
activating signals. We were also the first to provide experimental evidence that human PD-L2
similar to PD-L1 engaged the ITSM region on the cytoplasmic tail of PD-1 to inhibit TCR-CD3
activation. Through our work we also emphasized the incongruence between mice and human
in the context of PD-L2 immunobiology and cancer. We demonstrated that human PD-L2 did
not retain interaction with RGMb as observed in mice. In the course of our investigation, we
also found that co-expression of PD-L1 and PD-L2 on the same cell may lead to the formation
of a heterodimer that can induce a unique PD-1 inhibitory repertoire different from the
monomer ligands.

59
In the following pages I will discuss the impact of this dissertation and how our findings laid
the foundation for future investigations to harness the therapeutic potential of PD-L2 in
immunotherapy.
4.1. The paradoxical role of PD-L2: Mouse PD-L2 Vs Human PD-L2
Even though in recent years PD-L2 gained importance as a potential prognostic biomarker in
human cancers, immunologists hesitate to target the ligand to promote anti-tumor
immunity[126,133–139]. Previous studies of PD-L2 blockade failed to demonstrate
therapeutic benefit in orthotopic as well as transplantable murine tumor models[124]. The
clinical prospect of PD-L2 blockade was further dampened by reports that showed possible T
cell co-stimulatory functions of PD-L2 in mice[125,129]. Murine PD-L2 binds to RGMb to form
a signaling supercomplex with other proteins such as BMP and neogenin to facilitate the initial
T cell expansion in draining lymph nodes during respiratory tolerance induction. In a different
study, RGMb independent of PD-L2 was implicated in the development of airway inflammation
and airway hyperreactivity (AHR)[79]. A decade ago, a report demonstrated increased
expression of PD-L2 in the airways of asthmatic individuals and was correlated with severity
of asthma. However, the impact of PD-L2 as a causative or consequential factor of airway
hypersensitivity was not clarified. IL-4 is known to drive AHR and has long been associated
with pathogenesis of allergic disorders[140]. IL-4 is also known to selectively induce the
expression of PD-L2 but not PD-L1[141]. Preclinical investigations of PD-L2 and its role in
modulating immune responses in mice have been contradictory and assumed to be reflective
of its role in humans.
Our study was the first to demonstrate that mouse and human PD-L2 have functionally
different roles. We clearly showed that human PD-L2 binds to only PD-1 on T cells to inhibit
TCR-CD3 activation in human T cells. In our studies we primarily focused on sub-optimal
levels of T cell activation in the absence of CD28 co-stimulation in an attempt to replicate the

60
tumor microenvironment where co-stimulatory ligands are preferentially downregulated[142].
It will be interesting to evaluate the impact of PD-L2 on T cell responses in the presence of
CD28 co-stimulation since PD-1/PD-L1 complex is known to dephosphorylate the CD28
signaling axis over the TCR-CD3 complex[143]. We also showed that human PD-L2, unlike
mouse PD-L2 did not bind to RGMb.
While our results have conclusively shown that human PD-L2 does not bind to RGMb, future
studies exploring the possibility of new partners for PD-L2 on naïve T cells is warranted. Since
we tested the physical interaction between PD-L2 and RGMb exclusive of other proteins, one
can argue that PD-L2 and RGMb may need to form a complex with BMP/Neogenin to form
stable physiologically relevant interactions[129,144]. Even if it was true that we
underestimated the human PD-L2/RGMb interaction or the presence of alternate co-
stimulating binding partners of PD-L2, the widespread expression of PD-L2 in human cancers
reported in several research articles as well as in our analysis of cancer cell lines support our
result that PD-L2 is a solely inhibitory ligand in humans. This is in contrast to murine cancer
cell lines that do not express PD-L2 even when induced by cytokines. PD-L1 and PD-L2 as
members of the B7/CD28 superfamily of proteins are part of the paradigm that tumor cells
preferentially downregulate the expression of T cell co-stimulatory ligands and upregulate the
expression of co-inhibitory ligands to evade the immune system. Many human malignancies
associated with poor prognosis co-opt the expression of PD-L2 over PD-L1 that further denies
any potential costimulatory function in humans[126]. PD-L2 expression in human cancers was
proved to play a role in tumorigenesis and immune escape as well. In head and neck single
cell carcinoma (HNSCC) and oesophageal cancer patients PD-L2 expression correlated to
poor relapse free survival (RFS) and progression-free survival (PFS)[38,133,135]. PD-L2 is
also reported to be associated with neuroinvasion and low CD8+ TIL density in colon
cancer[145]. In the last 5 years, the concept of PD-L2 as a prognostic biomarker in human

61
cancers is gaining momentum, and our results clarifying the role of human PD-L2 further
bolsters this momentum.
Published studies delineating the biophysical properties of PD-L2 supported our conclusion
that mouse and human PD-L2 differ in their nature of regulation of T cell
responses[61,89,146]. Even though mouse PD-L2 shares ~70% amino acid sequence identity
with human PD-L2 it still differs in its mechanism of interaction with the PD-1 protein[147].
Human PD-L2 binds to PD-1 through a subset of amino acid residues that create a prominent
pocket absent in mouse PD-1/PD-L2 complex and provides for an attractive small-molecule
drug target[146]. Future investigations delineating the molecular and structural basis for PD-
1/PD-L2, PD-L2/RGMb, PD-1/PD-L1 interactions will help define potential hot-spots for
therapeutic interventions and curate the disruption of protein-protein interactions. Our findings
highlighted the limitations of traditional transgenic and transplantable mouse models of cancer
in the context of PD-1/PD-L1/PD-L2 immunobiology. The co-stimulatory function of murine
PD-L2 lacks relevance in human biology and as a result the translational opportunity of PD-
L2 blockade is misrepresented in traditional mouse models. Our work provides evidence in
support of the use of humanized mice to develop physiologically relevant preclinical models
in the future to optimally target the PD-1 signaling axis for clinical benefit.

62
4.2. The non-redundant role of PD-L2: Human PD-L1 Vs Human PD-L2
In normal human physiology PD-L1 is widely expressed in hematopoietic and non-
hematopoietic cells but PD-L2 is largely restricted to antigen presenting cells and the female
reproductive tract. Despite the 60% homology of amino acid residues between human PD-L1
and PD-L2, the ligands interact with different binding partners[60,89]. While human PD-L1
binds to CD80 and PD-1, PD-L2 interacts with only PD-1 on the surface of activated human
T cells[64]. Preliminary data in the lab demonstrated that PD-L1 and PD-L2 can interact with
each other in vitro.Previous surface plasmon resonance studies have demonstrated
significant differences in the association and dissociation characteristics of PD-1/PD-L1 and
PD-1/PD-L2 complex formation[89]. The distinct expression pattern of the ligands along with
differences in the structural mechanisms of interactions with cognate receptors argued
strongly in favor of non-overlapping roles of PD-L1 and PD-L2 in immune regulation.
Specifically in the context of anti-tumor immunity, the differential function of mouse and human
PD-L2 reported earlier in our study enabled us to speculate whether selective pressure during
evolution may have led to non-redundant PD-L1 and PD-L2 function in humans. A recent
study supported our theory and showed that PD-L2 evolutionarily originated from a gene
duplication event that diverged from PD-L1 at the level of placental mammals[89,148]. In the
past decade several research groups independently discussed the structural differences
between PD-1/PD-L1 and PD-1/PD-L2 complexes, but none could determine the molecular
and physiological consequence of the differences. We were the first to uncover that PD-L1
and PD-L2 engage PD-1 on human T cells to elicit distinct molecular mechanisms of inhibition
downstream to PD-1 in human T cells. Our discovery of differential signaling patterns induced
by PD-ligands was demonstrated through a robust multi-platform investigation of in vitro and
ex vivo assays of human T cells.

63
Key to understanding the PD-1 mediated inhibition is uncovering the mechanism underlying
the differential signaling mediated by PD-1. Is the differential signaling the result of unique
structural conformations of the PD-1/PD-L2 complex that induced unique signaling partners
downstream of PD-1? Or is it the functional consequence of a difference in the temporal
kinetics of PD-L1 and PD-L2 mediated PD-1 inhibition? One way we addressed this issue is
by performing site-directed mutagenesis of the signaling domains, ITIM and ITSM in the
cytoplasmic tail of PD-1. PD-L1 is known to engage SHP-2 phosphatase through the ITSM
domain of PD-1 to inhibit T cell activation, and the same was assumed to be true for PD-
L2[57,67,69]. However, our theory that PD-L2 preferred ITIM over ITSM was disproved when
we found that mutagenesis of Y248 in ITSM domain and not Y223 in ITIM domain reversed
PD-1 mediated inhibitory function. Even though in vitro the ITIM is known to activate SHP-2
like the ITSM, the failure to readily inhibit T cell indicates towards a possible conformational
change of PD-1 when bound to a ligand that limits the inherent potential of ITIM to recruit
SHP-2. Alternatively, it may be possible that the PD-1/PD-L1 complex induces ITSM to recruit
SHP-2 whereas PD-1/PD-L2 induces ITSM to recruit another family member such as SHP-1
or SHIP. This theory is supported by studies that evidenced SHP-2 independent mechanism
of PD-1 inhibition in T cells[70]. PD-1 is a transmembrane protein that engages its two known
ligands in unique conformations and a signaling competent cytoplasmic tail is the spark that
ignites the distinct signaling repertoires downstream. Our collaborator Dr. Wan-Lin Lo at the
University of Utah will perform co-immunoprecipitation assays with Jurkat T cells expressing
mutant forms of PD-1 to investigate the molecular partners bound to the cytoplasmic tail of
PD-1 when engaged by PD-L1 or PD-L2.
After validating our “omics” findings in functional assays we concluded that human PD-L2
binds to PD-1 to mediated weaker inhibition than PD-L1 resulting in a distinct signaling
repertoire downstream to PD-1. It is counterintuitive that a higher affinity ligand induces a

64
weaker signal through the same receptor. A possible explanation can be attributed to the 2-6
fold higher affinity of PD-L2 to PD-1 and the ability of PD-L2 to recruit PD-1 to the TCR
microclusters more potently than PD-L1[149]. Even though previous studies have opined that
the 2-6 fold higher affinity is insufficient to drive differential signaling, we speculate that the
significantly slower dissociation rate of PD-L2 off PD-1 may support the feedback loop of SHP-
2 mediated dephosphorylation of PD-1 cytoplasmic domains resulting in a weaker inhibitory
signal by the PD-1/PD-L2 complex[150]. Since our hypothesis on the role played by the
cytoplasmic domains in the differential signaling did not hold true, the mechanism underlying
the distinct PD-1/PD-L2 signaling remains an open question for further investigation.
4.2. The physiological relevance and therapeutic potential of PD-L2
Ultimately, it was pivotal for our study to elucidate the physiological relevance of the weaker
and distinct inhibitory signal induced by PD-L2 to inform future therapeutic interventions. We
discovered that the PD-1/PD-L2 complex inhibits T cells to a lesser extent and allows them to
be recovered more readily than the PD-1/PD-L1 mediated deeper inhibition of T cells. Our
findings showed that in vitro human T cells inhibited by PD-L2 recovered and produced higher
levels of IL-2 and TNFα that were comparable to uninhibited T cells. Future investigations
focused on evaluating the impact of PD-L2 on the ability of tumor infiltrating T cells to regain
anti-tumor potential will be seminal for immunotherapy against cancer. The more reversible
anergy mediated by human PD-L2 may also have a role to play in physiological contexts other
than cancer like chronic viral infection, mucosal immunity, and autoimmunity[83,151]. Our
findings may also help delineate the functional consequence of PD-L2 expression in maternal
fetal tolerance (MFT) since PD-L2 like PD-L1 is expressed in the placenta and is finely tuned
as the pregnancy progressed through the trimesters[84,85,88].
Our study primarily focused on the impact of PD-1/PD-L2 signaling on T cell responses and
provided the rationale to investigate the presence and consequence of the differential

65
signaling mediated by PD-L2 through PD-1 in other immune and non-immune cells as well.
More recently the expression of PD-1 has been appreciated in Tregs, tumor cells, NK cells,
dendritic cells and myeloid cells like macrophages[59]. The precise function of PD-1 signaling
axis in each of these cells is yet to be delineated. We provide the premise to perform these
future investigations using PD-L1 as well as PD-L2 as the inducer of PD-1 in their
experiments. This will ensure that we are not underestimating the differential role PD-1
engagement by PD-L1 and PD-L2 in cells other than T cells.
Even though it’s been more than 20 years since its discovery, there remains no disclosed
effort to directly target human PD-L2 therapeutically. This may be due to preclinical murine
models that inadequately represent the function of human PD-L2 or the assumed functional
redundancy with PD-L1 that our study conclusively debunks. Through our work we
established the rationale for PD-L2 to share the spotlight with PD-L1 to achieve optimal anti-
tumor immune responses in the clinic. Can higher expression of PD-L2 in human cancers be
correlated with increased potential of tumor infiltrating T cells to recover its cytotoxic potential
on account of the more reversible anergy mediated by PD-1/PD-L2 interaction? Does this
proposed mechanism explain several recent scientific studies that demonstrate the ability of
PD-L2 expression in human cancers to be more predictive of response to PD-1 blockade
therapy than PD-L1? In the last decade novel antibody-engineering techniques enabled
scientists to engage the innate arm of the immune system (NK cells) to deplete the
immunosuppressive stromal cells in the tumor microenvironment and support cytotoxic T cell
tumor infiltration and anti-tumor function[152]. The restricted expression pattern of PD-L2 on
tumor cells and immunosuppressive stromal cells gives us an opportunity to arm our blockade
antibodies with antibody dependent cellular cytotoxicity potential (ADCC) and strategically
reprogram the tumor microenvironment to support anti-tumor immunity.

66
In conclusion, the work demonstrated in this dissertation is to our knowledge the first study to
discover the unique mechanisms of PD-1/PD-L1 and PD-1/PD-L2 mediated inhibition of T cell
function. Our findings broadened the field’s understanding of the PD-1 signaling axis and may
have implications in other PD-1 expressing cells as well. We lay the foundational block for
future investigations to study the PD-1 signaling axis in the context of both ligands, PD-L1 and
PD-L2 to gain a comprehensive perspective of the underlying biology. Our study did not
consider the recently appreciated putative signaling domains in the cytoplasmic tails of PD-
L1[153,154]. While we studied the influence of the differential engagement of PD-1/PD-L1 and
PD-1/PD-L2 downstream to PD-1 in T cells, future studies should investigate the impact on
the downstream signaling of PD-L1 and PD-L2. We demonstrate that the PD-1/PD-L1/PD-L2
signaling axis is not binary in its function, instead PD-1 can suppress T cell function to varying
degrees of inhibition depending on the ligands available for ligation. We are the first to show
that PD-L1 induces T cells into a deeper state of exhaustion whereas PD-L2 weakly inhibits
the T cells to a more reversible state of anergy. In the future it will be interesting to see the
relevance of PD-L2’s reversible state of anergy in the context of tumor immunology. Can we
reverse the inhibition mediated by PD-L2+ tumors more readily on account of the reversible
state of anergy? As we gain deeper insights into the structural and mechanistic biology of the
PD-1/PD-L1/PD-L2/CD80 signaling axis, we will be able to rationally curate future
therapeutics against cancer such that we disrupt specific arms of the signaling axis while
retaining those that will protect the patient from immune related adverse events.

