


Patient Risks and Clinical Care Disruptions in
Rural Hospital Mergers
Section 1: Foundation of the Study and Literature Review
Introduction
The world of the U.S. healthcare system is experiencing many wave changes,
among them the trend for rural hospitals to be taken over by sizeable hospitals that are
part of larger healthcare systems (Henke et al., 2016; Rural Health Reform Policy
Research Center (RHRPRC), 2014). The broad pattern of large health systems acquiring
and consolidating rural hospitals may contribute to increased rates of mortality, and
hospitalizations for rural patients with conditions, such as cancer, asthma and pneumonia,
which are preventable if patients receive the appropriate and convenient quality of care
(Hass, Gawande, & Reynolds, 2018). The absorption of rural health systems also may be
at least partially responsible for the higher incidence of other chronic health conditions,
such as hypertension, heart disease and emphysema, among rural residents (Holmes,
2015). A recent collaborative study by researchers from the Harvard-Affiliated Health
Systems identified hospital mergers and affiliations as an emerging area of patient risks
emanating from critical sources such as new patient populations, unfamiliar infrastructure
and unique setting for clinicians (Hass et al., 2018) While there are no indications that the
pace of hospital and health system alliance and acquisitions will diminish, there has been
little attention paid to patient safety in rural hospital mergers (RHMs), which account for
up to roughly half of all U.S. hospitals (Brown et al., 2016).

Since the execution of the Affordable Care Act of 2010, there has been a quick
surge of hospital consolidations- mergers and acquisitions (Pope, 2014). A recent analysis
by Hall (2018) revealed that 30 hospital and health system partnership transactions were
completed in the first quarter of 2018, which is up more than 11% from the first quarter
of 2017. Williams Jr, Thomas, Howard, and Pink (2018) described the number and
geographic distribution of 380 RHMs from 2005 through 2016 in over 24 U.S. states as
significant, with potential concerns fueled by cost pressures, technological advances, and
patient demands.
Although such trends are substantial, they do not capture the full extent or impact
of the affiliations of rural health systems on the quality of care after such mergers have
occurred. As U.S. rural healthcare continues to transform across the country, the North
Carolina (NC) RHRPRC (2014) predicted that over 700 more hospitals that are rural are
at risk of either being taken over or closed within the next 10 years. Despite playing the
leading role in the provision of various types of health services to 60 million U.S.
citizens, hospitals in the rural United States face a unique set of challenges and are often
coerced to make difficult decisions where patient safety may be compromised (American
Hospital Association [AHA], 2018).
Advocates for hospital mergers often present one side of the argument: alliances
are necessary to lower costs and improve efficiency and access to care. Noether and May
(2017) reported that when healthcare organizations begin planning about mergers or
acquisitions, network development leaders — whose experience is business oriented and
not in medicine — tend to be at the forefront of the dialogues. Perhaps, healthcare

executives with little proficiency in patient safety are customarily responsible for
executing healthcare mergers and acquisitions (Haas et al., 2018). Because the incentive
is often financial rather than clinical, the goals and responsibilities for patient safety and
quality of care are often overlooked (see., Haas et al., 2018; Kaufman et al., 2016).
Nevertheless, system expansions or mergers can increase market power and broaden the
capacity of health services to patients, at least in the short term; however, without
planning, such changes can cause significant patient risks and may also create a set of
other challenges such as increases in medical malpractice, delays in treatments, fines, and
penalties (Johar, & Savage, 2014). Although healthcare organizations have invested vast
sums of money in mergers and acquisitions, the quality of care provided after such
consolidations frequently falls far short of what is optimal (Noles, Reiter, Sheps, &
Boortz-Marx, 2015).
By focusing on four aspects of leveraging organizational synergies: (i.e. change
management, governance mechanisms, system integration best practices, and the role of
clinical leadership), I sought to add the knowledge needed to promote the adoption of the
patient safety culture model in RHMs. This investigation was anticipated to fill a gap in
the literature by exploring the correlational of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical outcomes for rural
patients. Trying to discern the relationship between rural communities, and hospital
mortality through conducting a performance comparison of RHs post mergers could
prompt policymakers to identify strategies for future quality improvement efforts that
narrow identified gaps. Such specifics would not only allow policymakers to better

prioritize the best integration practices likely to improve quality of care but would begin a
new era towards a more comprehensive redesign of better care pathways that would
reduce mortality rates in rural communities.
In this study, I investigated the aspects of patient risks and CCDs in RHMs. While
different scholars have studied issues of patient risks and clinical discourse, not much
attention has been placed on how RHMs contribute to the patient risks and clinical
discourse. This first section of this study comprises the introduction, background to the
problem statement, purpose of the study, significance of the study, theoretical foundation
for the study, definition of terms, nature of the study, secondary data types and sources of
information, a literature review related to critical variables and/or concepts, definitions,
research questions and associated hypotheses, assumptions, scope and delimitations, and
a summary.
Background of the Study
Unsafe healthcare is always one of the challenges of the U.S. healthcare delivery
system and a well-recognized health issue, usually listing among the top three causes of
deaths in the United States, with rural residents experiencing more significant hardship
(NC RHRPRC, 2014; Taylor, 2019). As the broad trend of large health systems acquiring
and consolidating rural hospitals is expected to continue, serious questions about the
impact the mergers will have on access to high-quality health care services in U.S. rural
communities have been raised (Hass et al., 2018). Infrastructure changes and
organizational complexities from healthcare system mergers not only can challenge
clinicians but can cause risk to patients (Noles et al., 2015). The idea that merging

healthcare systems and processes may be deceptive and yield medical errors and harm
patients is not a new phenomenon.
Recent estimates suggest that approximately 97% of U.S. landscape belongs to
rural counties, and 60 million people (roughly 19.3% of the population reside in these
areas (U.S. Census Bureau, 2016). According to the Centers for Disease and Prevention
Control (CDC), an estimated 40% of rural residents reported missing a usual source of
care, of which 15% indicated travel to the next hospital or financial reason for requiring
regular access to quality of care (CDC, 2017). These numbers are also elevated among
racial and ethnic minority groups compared with White populations (CDC, 2013).
Among the crisis of access, equity, economic complexities, and shortages of providers, a
disproportionate number of rural hospitals across the United States are modified through
mergers and acquisitions (NC RHRPRC, 2014; Noles et al., 2015).
While numerous proposals to improve the U.S. rural delivery services have been
initiated, substantial differences across a range of quality domains remain for rural
residents compared with urban and suburban counterparts (Ely, & Hoyert, 2018). Even
though previous studies have shown some anticipated benefits of hospital mergers (e.g.
improved financial performance, service consolidation, and operating efficiencies), there
has been less progress in improving quality, and reducing health inequities and mortality
rates (Noles et al., 2015).
Even though much is known about the financial influence of health system
mergers and acquisitions, there has been little evaluation of the CCDs and patient safety
risks (PSRs) that hospital mergers and acquisitions have on rural patients. The recent

decline in life expectancy, the recent increase in chronic disease deaths, and the
widespread of other diverse chronic disease morbidity and mortality in the rural United
States, with substantial differences in quality domains, raise the issue of whether RHMs
are addressing the health of its rural population effectively (Crossman et al., 2017; Health
Resources & Services Administration, 2017; Kessler, & Alverson, 2013).
Problem Statement
In the United States, approximately 60 million people live in rural communities,
including millions of Medicare and Medicaid beneficiaries (AHA, 2018). Nearly 1 in 5
U.S. citizens who live in rural areas rely heavily on rural hospitals as the cornerstone of
their health system during emergencies and disasters (Abuse & Administration, 2016).
Because such hospitals care for most seniors with complex chronic diseases, such as
diabetes, cancers, strokes, and lower respiratory complications, these institutions
encounter regulatory and financial pressures that increase vulnerability to cutbacks and
patient safety risks (CDC, 2017). The American Academy of Family Physicians (2015)
noted several challenges that rural U.S citizens face, including living in communities with
disproportionally higher famine rates, having more chronic conditions, being uninsured,
experiencing a disintegrated healthcare delivery system with a shrinking health
workforce, and lacking access to high-quality health care services.
The number of RHMs has increased significantly in recent years. This broad
pattern of large health systems acquiring and consolidating rural hospitals is expected to
continue, raising questions about the impact the mergers will have on access to
highquality health care services in rural communities. According to Kaufman (2018),

healthcare organizations announced a total of 115 transactions in 2017, representing a
13% surge compared to the previous year. From 2005 to 2016, more than 380 rural
hospitals in the United States were merged, and the activities have affected the delivery
and availability of services as joining hospitals work toward greater efficiency in cost
control (Williams Jr et al., 2018).
As the rural healthcare system is abruptly consumed through mergers, the
aftershock creates permanent gaps in access to quality of care between rural and urban
U.S. citizens (Kaufman et al., 2016; Worek, 2017). Numerous studies have highlighted
that rural patients with complex chronic illnesses have shown worse patient outcomes
than their urban counterparts (CDC, 2013; Unger et al., 2018). McCullough and Flowers
(2018) noted inferior mortality and life expectancy rates for the rural United States, with
the most substantial disparities gap noticed in access to quality of care and patient safety
risks. Noles et al. (2015) reported that high inpatient mortality in state hospitals in
California was positively associated with hospital mergers. Previous studies have shown
that there is the potential for both positive and negative effects on patients, communities,
and employees (Johar, & Savage, 2014; Noles et al., 2015). However, when health
systems integrate, the work processes and organizational culture; recruitment structure of
physicians, nurses, and other healthcare providers, as well as the overall delivery of
healthcare within the merged entity, changes (Vogel, & Hadfield, 2017).
Increasing evidence suggests that 440,000 U.S. citizens are dying annually from
the poor quality of care in the hospital settings, and rural inhabitants experience more
significant health threats than any other group in the United States (James, 2013). Moy,

Garcia and Bastion (2017) expressed that preventable deaths were about 50% higher in
rural areas, partly because of higher risk due to lengthy trips to specialty and urgent care
or other social, demographic, and economic factors (see Liu, Singer, Sun, & Camargo,
2011). Adding to these statistics, the U.S. National Vital Statistics Systems [NVSS]
(2017) reported that the newborn death rate is more than 25% higher in rural communities
compared to metropolitan areas. Rural U.S. citizens are more likely to die from
potentially preventable health threats than their urban counterparts (CDC, 2017). The US
Census Bureau (2016) further asserted that there had been significant rural-urban health
disparities in mortality rates, life expectancy, the incidence of diseases, and morbidities.
The noticeable gap in health between rural and urban U.S. citizens shows that lower
quality of care is one of the most pressing patient safety concerns, specifically in RHMs,
that is demanding more leadership and action (NC RHRPRC, 2014).
Patient risks and CCDs could be the probable foremost reason for the discrepancy
in both adult and infant mortalities in rural areas (U.S. NVSS, 2017). The exact scope of
the problem is displayed by the fact that more than 65%, which is approximately 286,000
deaths each year in rural communities, are entirely preventable (Agency for Healthcare
Quality and Research [AHQR], 2018; Ely et al., 2018). Arguably, the noticeable gap in
health between urban and rural communities is not something new, particularly to the
U.S. healthcare system (Moscovice, Johnson, & Burstin, 2017). However, various
researchers have highlighted this worsening gap between health outcomes in urban and
rural inhabitants of the United States (James et al., 2017; Noles et al., 2015; Unger et al.,
2018). Nevertheless, between 2005 and 2016, more than 380 RMH transactions have

been completed nationwide, with little data reported on the clinical impact of the mergers,
or the impact on access to care within rural communities. Although much is known about
the financial effects of hospital mergers, research shows partnerships and transactions
might create a permanent gap, which leaves perpetual patient risks and clinical
disruptions (American’s Health Insurance Plans, 2014; American Health
Information Management, 2012; Hayford, 2011; Jennings, 2008; Johar et al., 2014;
Noether, & May, 2017). Among other challenges, such as long distances between health
care facilities and trauma centers; cost of access to specialized care, and patient
risksrelated to changes in patient populations, infrastructure, and clinical practice settings,
the responsibility for safety and quality when entities merge may be unclear (Capps,
Dranove, & Ody, 2018; Haas et al., 2018; Henke et al., 2016). Perhaps, the interruption
induced by integrating two independent facilities may negatively impact quality,
particularly in the immediate aftermath of the merger (Hayford, 2011).
Purpose of the Study
In this study, I employed a quantitive approach to describe patient risks and
disruptions of clinical care in RHMs. The principal objective of this correlational study
was to examine the potential association of healthcare transformation change, in
structures, processes, organizational culture, and values on clinical outcomes for rural
patients during mergers. A secondary goal of the study was to enhance the understanding
of the incidence of patient risks and clinical turbulence after mergers as a basis to reduce
them. To date, while many studies have focused on the association between hospital
consolidation and the financial aspects, no previous studies have been conducted to

explore or identify particular areas where system complexities handicap or delay the
adaption of a holistic patient safety culture in RHMs (Noles et al, 2015). To bridge this
gap in the published literature, I focused on three aspects of leveraging organizational
synergies: governance mechanisms, system integration best practices, and the role of
clinical leadership.
Using the Medicare Mortality Ratings Databases, Hospital Compare, and Hospital
Evaluation Databases, which tracked mergers in rural hospitals in the United States from
20102018, in this study I specifically assessed the performance of rural hospital alliances
regarding structures, processes, and outcomes and evaluated the correlation between
quality domains. I used the patient outcome measures of mortality and readmission rate to
study the effects of hospital alliances on quality of care. Understanding the relationship
between hospital mortality and the potential performance comparisons of rural hospitals
post mergers could prompt policymakers to identify opportunities for future quality
improvement efforts that narrow identified gaps.
Significance
I anticipated that the findings of this study would fill a gap in the literature by
focusing on the relationship of healthcare transformation changes in structures, processes,
organizational culture, and values on clinical outcomes for rural patients. Trying to
understand the relationship that exists between rural communities and hospital mortality
through conducting a performance comparison of RHs post mergers could prompt
policymakers to identify opportunities for future quality improvement efforts that narrow
identified gaps. By defining quality improvement initiatives and, facilitating this kind of

feedback and discussion, the findings of this study may present healthcare legislators with
potential tools to highlight low points in patient care of which the U.S. healthcare system
may not have previously been aware (see Institute of Medicine [IOM], 2012;
Manghani, 2011).
The results of this study could make substantial contributions to the field of health
care administration and may result in significant social change through recognizing rural
the population as a separate group in research, analyzing patient risks impacting this
group and comparing them with other factors that attribute to the disparity of accessing
quality of care and mortality rates, which will significantly remedy clinical challenges
and improve patient safety (see Ackerman et al., 2018; James et al., 2017; Khalil et al.,
2017). Various network developmental leaders, practitioner administrators, and
policymakers could look at the findings of this research study to identify effective
integration practices for hospital mergers. In addition to achieving better quality of care
and minimizing preventable deaths, improvement in clinicians’ engagement in hospital
consolidations may sustain continuity of care and provide more opportunities for
financial stability in the rural healthcare system.
Framework of the Study
The conceptual framework for this study was grounded on Donabedian's (2005)
theory of epistemological perspective. According to Donabedian's epistemological
analysis for quality management, improvements in the structure of care should lead to
improvements in clinical processes that should improve patient outcomes (Moore,
Lavoie, Bourgeois, & Lapointe, 2015). I used Donabedian’s quality improvement model

to assess the performance of rural hospitals post mergers regarding structure, process, and
outcome and evaluate the correlation between quality domains. The structure includes all
the factors that affect the context in which care is delivered, the process describes the sum
of all actions that make up healthcare, and outcomes denote all the effects of health care
on patients or populations. The goal of this study was to further explore the principles for
successful health systems integration in critical areas such as restructuring, organizational
flexibility, and adaptation (see Grol et al., 2007; Suter, Oelke, Adair, & Armitage, 2009).
Application of Donabedian’s (2005) philosophical theory to evaluate and
transform the social conditions of the targeted rural hospitals as well as testing the
processes in place that protect patients and procedures of hospital cultures involved,
clearly supports that the method used strongly affect the conclusions to be drawn. Given
the inherent complexities of the U.S. healthcare system, a theoretical framework that
requires a holistic approach to identify specific areas where system complexities slow or
inhibit progress could prove beneficial to a study (see Hempel, Gibbons, & Ulloa, 2015;
IOM, 2011). Donabedian’s theoretical work offered an in-depth description process
through which I could articulate a definite need for quality improvement initiative to
ensure the level of readiness and adaptability necessary for quality patient safety and
provide a useful outlet for minimizing CCDs. Further, the theory may provide
decisionmakers with system-level indicators of quality and assist in exploring strategies
that network development leaders may use to improve organizational performance.

Definitions
Clinical care disruptions/Clinical Discourse (CCDs): Health care services
characterized as turbulent, hectic conditions, more interruptions, and distractions resulting
from the rapid growth of large health care corporations, which has altered organizational
structures and dynamics as well as continually changed health policies (see Jennings,
2008).
Clinical leadership measures: Measures that reflect the attributes of ensuring that
the values and cultures of two different entities are aligned with the common goal of
improving the quality of care (see Sarto, & Veronesi, 2016).
Hospital mergers/consolidations: The concept of bringing together individual
hospitals via complete changes in the actual ownership. Combining administrative and
organizational resources of two or more health care facilities can occur through either
merger or acquisition (Hill Jr., 2018).
Hospital structures-care processes: These processes consist the way healthcare
systems and processes work to achieve the desired outcome. This may include the length
of time a patient waits for a clinical audit, ensuring required standards of care are met, or
making sure that staff members wash their hands and report incidents (AHRQ, 2011).
Governance Mechanisms: Measures that reflect strategic controls, policies, and
guidelines that drive the organization toward its objectives and further demonstrates the
relationship between the characteristics of the health systems that have merged and the
leadership processes and their consequences to the health and welfare of individuals and
the community (Baker, Denis, Pomey, & MacIntosh-Murray, 2010).

Patient Safety Risks (PSRs): Hazards that cause or can cause healthcare-associated
harm or injury (Jennings, 2008).
Preventable Adverse Events (PAEs): Care that fell below the standard expected of
physicians in their community (see Barach, Jacobs, Lipshultz, & Laussen, 2015); Hodges,
Spiller, Casavant., Chounthirath, & Smith, 2018).
Quality domains: The IOM defines quality domains as care-oriented task that
encompasses the following key indicators of care -safety effectiveness, patient
centeredness, efficiency, timeliness, and equitable (AHRQ, 2016).
Rural Hospitals (RHs): These are hospitals that are found within the rural
localities, far away from towns (NC RHRPRC, 2014).
System integration best practices measures: Measures that helps organizations to
identify unintended consequences of change known as organizational balancing
measures. (Suter, Oelke, & Armitage, 2009)
Research Questions and Hypotheses
In this study, I developed the following four research questions and corresponding
hypotheses about the association between organizational synergy ramifications, PSRs,
and CCDs post RHMs as determined by Donabedian’s model of care to assess the
outcomes of quality of care in rural health centers (see Lukas et al., 2008).
RQ 1: Is there an association of healthcare transformation changes in structures,
processes, organizational culture, and values on clinical outcomes for rural
patients?

H01 —There is no association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical
outcomes for rural patients.
Ha1 —There is an association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical
outcomes for rural patients.
RQ2: What is the relationship between governance mechanisms and patient
outcomes in RHMs?
H02 —There is no relationship between governance mechanisms and
patient outcomes in RHMs.
Ha2 —There is a relationship between governance mechanisms and
patient outcomes in RHMs.
RQ3: How do best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and the
process of care?
H03—Best practices do not facilitate quality-focused initiatives and do not
contribute to eliminating unintended patient risks associated with
structural changes and the process of care.
Ha3 —Best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and
the process of care.

RQ4: What is the relationship between clinician leadership and the quality of care
outcomes in RHMs?
H04— Clinical leadership in RHM and acquisition deals is not a
significant predictor of quality of care outcomes.
Ha4 —Clinical leadership in RHM and acquisition deals has a significant
relationship with the quality of care outcomes.
Nature of the Study
In this study, I conducted a secondary data review in which relevant data were
collected to determine patient risks and CCDs in RHMs. The focus was to confirm or
validate existing relationships and yield generalization that could be applied in the
development of some critical theories. Trying to understand the link between rural
communities and hospital mortality through conducting a performance comparison of
RHs postmergers could prompt policymakers to identify opportunities for future quality
improvement efforts that narrow identified gaps. In this study, I gathered data from
Medicare Mortality Ratings Databases, Hospital Compare, and Hospital Evaluation
Databases from 20102018 to research the performance differences. The data collected
from the secondary documents were entered into Statistical Package for the Social
Sciences (SPSS) computer software and analyzed as considered appropriate. The specific
variables investigated were RHMs (i.e., the independent variables) and patient risks and
clinical disruptions (i.e., the dependent variables).

Literature Review Related to Key Variables and/or Concepts
Several scholars have conducted studies on the topic of patient risks and CCDs in
RHMs. In this literature review, I considered the implications of care fragmentation that
dominate the more obvious health care crisis and the need for integrative solutions in
hospital mergers (see Stange, 2009). To begin with, Noles et al. (2015) and Burkey,
Bhadury, Eiselt, and Toyoglu (2017) highlighted and studied the characteristics of RHs
that closed, merged, or were acquired to see how they coped with structural changes,
what they have in stock, and what other predictors of success or failure related to access
to care. Mainly, Burkey et al. discussed the effects of hospital closures on equity and
examined whether rural residents are disproportionately affected by hospital closures.
Noles et al. used data from Irving Levin Associates (ILAs)' Healthcare Merger, and
Acquisition Report and Medicare Cost Reports from 20052012. The researchers then
applied logistic regression to identify specific factors that tend to predict mergers, while,
at the same time, using multiple regression to examine different hospital measures after
mergers and acquisitions.
Their empirical findings cited the variations in patient needs, demographic shifts, and
facility conditions as reasons for closures. Noles et al. further identified changes in rural
hospital financial performance, staffing levels, and inpatient services as predictive factors
of mergers; however, the methodology they used was not apparent.
Hass et al. (2018) cited three factors that can create significant downstream
conditions that can result in multiple failures. They highlighted the need for healthcare
leaders to use system data to plan for unexpected downstream situations driven by

changes in both organizational and governance processes. However, this information was
based on an individual opinion without any form of scientific evidence.
Hospital mergers are paradigmatic complex entities, and their ability for
collaboration, commitment, and leadership among clinicians can be obstructed by culture
dynamics, value boundaries, and changing government regulations. Grol, Bosch,
Hulscher, Eccles, and Wensing (2007) offered different theoretical assumptions to plan
for and manage the impact of quality improvement initiatives in complex changing
environments, and these were possible theories considered for application in the present
study. Grol et al. discussed the theories of leadership in management and total quality
management, often known as continuous quality improvement, as tested mechanisms
when redesigning multidisciplinary care processes and promoting a quality safety culture
in a changing environment. Millar, Mannion, Freeman, and Davies (2013), on the other
side, elucidated the role of a hospital board’s oversight of patient safety and revealed
several approaches to be explored in diffusing the complexities and ambiguities related to
evidence-informed governance and quality practices in changing structural environments.
Brown et al. (2016) presented different views on the successful implementation of
clinical networks about the reorganization of healthcare services in hospital
consolidations. Johar et al. (2014) and Kaufman et al. (2016) cited problematic
downstream conditions of patient risks attributable to the rapid surge of RHMs and
affiliations. Both groups of authors offered unique insights into patient wait time effects
and variations in hospital performances.

Experts of healthcare mergers and acquisitions argued that structure changes
involving cultural assimilation, process, integration, technology, and system integration
are essential to survive in the shifting industry landscape. (see Jennings, & Hughes,
2008). Williams Jr. et al. (2018), on their part, examined the pattern of mergers of rural
hospitals across the United States. from 20052016 and looked at the financial impact of
merging and discussed the effect on access to care within rural communities. The authors
also identified significant concerns such as reduced negotiating power with insurers,
centralized governance, and outsourcing of support services as factors that could create
an unnecessary burden to clinicians and confusion among patients. Ackerman et al.
(2018) examined proposed patient safety measures for capturing patient safety variations
in ambulatory care in safety net health systems (SNHS). The authors reported the
problems faced by SNHS, rural hospitals, and other providers, and found that lack of
active participation of key stakeholders such as patients, clinicians, staff, data system
professionals, and health system leaders, remains an impediment to quality improvement
initiatives.
Secondary Data Types and Sources of Information
Data in this study were based on information collected from the 50 states, and are
publicly available on Medicare Hospital Compare. Mortality and hospital readmission
data on specific medical conditions and patient characteristics, which covers all 50 states
excluding the District of Columbia, were included in the study. Patient morbidities and
ethnicity information came from the Centers for Medicare and Medicaid Services (CMS)
Hospital General Information File (i.e., HOSArchive_Revised_Flatfiles_20190702). Data

on hospital characteristics were obtained from NC RHRPRC and ILAs Healthcare
Mergers & Acquisition reports collected from 2010 through 2018, in which I identified a
total of 380 rural hospitals that have merged or acquired. Both NC RHRPRC and ILAs
maintains a publicly available map for tracking and counting RHMs and closures.
Additional data for hospital characteristics were collected from the Medicare Provider of
Service files and the Healthcare Cost Report Information System.
I assessed data from Hospital Consumer Assessment of Healthcare Providers and
Systems measures publicly reported on Hospital Compare to measure hospital
performance on clinical process and patient experience composite measures (Casey,
Hung, Evenson, Distel, & Moscovice, 2015). The performance composite measures
consisted of routinely collected CMS outcome measures were grouped into six categories
weighted by importance: mortality, safety of care, rehospitalizations, patient experience,
effectiveness of care, and timeliness of care. To minimize the susceptibility in these
measures of quality, I grouped the six separate outcome measures followed by CMS into
three composite outcome indices: one for 30-day mortality, one for 30-day readmission,
and one that combines both mortality and readmission measures.
My digital procedure of collecting secondary data from scholarly databases was
comprised of entering specific words, such as patient risks, clinical care disruptions, and
rural hospital mergers. I only referenced websites that showed relevant results, or
conventional sources of secondary data for social sciences such as national censuses,
information collected by government departments, and other organizational records
related to the topic under study. The exclusion and inclusion criteria for this review of the
literature was only journals written in English and those not published more than 7 years

ago being considered for analysis. By performing secondary data analysis, I adequately
gathered relevant information related to specific patient risks and CCDs in RHMs.
For this study, I assessed secondary data collected by government public services
departments, libraries, and censuses, such as the U.S. Census, the CDC, the CMS and the
U.S. NVSS. The sources were obtained through the use of search engines that enabled
access to different articles plus some other sources of information that were needed for
the study. The search engines, in this case, did allow access to academic essays and
journals, e-books, and papers that contained content on the topic. Relevant articles and
ebooks were also reviewed after first gaining access to the relevant abstracts and articles,
through entering the keywords that were selected for the study. Upon acquiring enough
resources and materials, I checked the information, data, and records deemed relevant.
Assumptions
In this study, I assumed that RHMs have both positive and negative patient risks
and CCDs. I also assumed that relevant data would be obtained as far as the topic is
concerned. Another assumption that the data collected from Medicare Mortality Ratings
Databases, Hospital Compare, and Hospital Evaluation Databases on PSRs were reported
precisely and correctly, and the use of the current studies was critical to drawing
significance findings.
Scope and Delimitations
I constructed this study to analyze the relationship which is there between rural
communities and hospital mortality through conducting a performance comparison of
RHs post mergers with the desire to identify opportunities for future quality improvement

efforts that narrow identified gaps. The extent of the study was limited to patient risks and
clinical discourse in RHMs. In this study, I conducted a quantitative analysis in which
relevant, quantitative, and secondary data from Medicare Mortality Ratings Databases,
Hospital Compare, and Hospital Evaluation Databases were collected to determine
patient risks and clinical discourse in RHMs.
Limitations, Challenges, and Barriers
Various studies have reported the problems faced by researchers when selecting
their research methodologies. As outlined by Saunders, Lewis, and Thornhill (2009), the
research methodology serves as the foundation of the study. With the use of the
quantitative methodology, there were at least three potential challenges that could have
resulted in limitations that may have been beyond my control. The lack of resources for
data collection may have resulted in limited understanding and, especially, the resources
needed to perform an in-depth quantitative investigation (see Younus, 2014). Quantitative
study demands comprehensive statistical analyses, which may be challenging to perform
for researchers from non- mathematical backgrounds. Finally, to achieve in-depth quality,
a quantitative study may involve extra time, investment, and resources to refine the
results (Saunders et al., 2009). To reduce some of the barriers, I used publicly available
secondary data from Medicare Mortality Ratings Databases, Hospital Compare, and
Hospital Evaluation Databases (2010–2018) to research the patient risks and CCDs in
RHMs. Due to its exposure and public cross-examination, secondary data collected from
Medicare Mortality Databases and Hospital Compare, and Hospital Evaluation Databases
have a preestablished degree of validity and reliability.

Significance, Summary, and Conclusion
In this first section of the study, I introduced the study, and provided the
background to the problem, the purpose of this study, the theoretical framework, the
nature of the study, a literature review related to critical variables, secondary data types
and sources of information, research questions with associated hypotheses, assumptions,
scope and delimitations, limitations, and challenges and barriers. Safeguarding patients in
health care settings is cornerstone to achieving high-quality health care for the U.S.
population (IOM, 2001; Sacristan, 2013). Rural inhabitants of the United States are
approximately 50% more likely to die from preventable causes (James, 2013). Rural
communities still experience a newborn death rate 25% higher than their urban
metropolitan counterparts (Moy et al., 2017; NVSS, 2017). Many of these PAEs are
linked to the poor quality of care (CDC, 2017).
Evaluating these risk factors and identifying the national goals that aim to increase
patient safety through best practices focused on healthcare-associated adverse events in
RHMs could generate improved clinical outcomes (Darker, Nicolson, Carroll, & Barry,
2018). Hence, understanding the relationship between rural communities and hospital
mortality through conducting a performance comparison of RHs postmergers could
prompt policymakers to identify opportunities for future quality improvement efforts that
narrow identified gaps.
Although numerous proposals to improve the U.S. rural delivery services have
been initiated, substantial differences across a range of quality domains persist for rural
residents compared with urban and suburban counterparts (see Buettner-Schmidt, Miller,

& Maack, 2019). Ely et al., 2018). There has been little evaluation of the CCDs and PSRs
on hospital mergers and acquisitions for rural patients based on the Donabedian’s
conceptual framework of quality of care through the triad of structure, process, and
outcome (see Ayanian, & Howard, 2016; Pazargadi, Abedsaeedi, Majd, & Lankshear,
2008). The findings of this quantitative research study, therefore, fill the gap that exists in
the current literature and could offer an in-depth description process that can be used to
articulate a definite need for quality improvement initiatives to ensure the level of
readiness and adaptability necessary for quality patient safety, and provide a useful outlet
for minimizing CCDs (see Moore et al., 2015). Assessing the association of structure,
process, and outcome variables in RHMs will not only help to reduce PAEs, but it will
also provide decision-makers with system-level indicators of quality and assist them in
exploring strategies that can be used to improve organizational performance. In Section 2
of this study I presented the research design and the specific procedures used in
conducting this study.
Section 2: Research Design and Data Collection
Introduction
Since 2010, over 380 rural hospitals have merged, affecting access to quality of
care and triggering complex PSRs and associated CCDs (Williams Jr. et al., 2018). The
burden affects nearly 60 million people who reside in rural counties across the United
States including millions of Medicare and Medicaid beneficiaries (CDC, 2017).
Numerous studies have recognized the multiple hurdles that rural residents encounter
when accessing medical services, including a disintegrated healthcare delivery system,

stretched and diminishing rural health workforce, and unaffordable medical costs (AMA,
2018). The AHRQ (2018) and NC RHRPRC (2014) both acknowledged that hospital
mergers and acquisitions are modifying the face of health care in rural communities
across the United States.
With the significant expansion of hospital mergers or acquisitions, there is a
problem with the quality, efficiency, and patient safety in the U.S. rural healthcare
delivery, mainly related to RHMs (CDC, 2017; NC RHRPRC, 2014; Unger et al., 2018;).
Tens of millions of rural residents are impacted by such transactions each year (Hass et
al., 2018). Health care delivery in rural areas of the United States is mostly fragmented,
and because of its fractured nature combined with the health care needs of rural residents,
who may be at higher risk for multiple chronic conditions that require treatment from a
team of providers, coordinating care among specialists can be strenuous (see AHRQ,
2012; CDC, 2017; Davis et al., 2015). This can also result in unnecessary and costly
duplication of services as well as an increased risk of medical errors (see Berg, &
Grimeland, 2013). The disruption resulting from integrating two independent facilities
with opposite values is a system that often is costly and less effective at meeting the
needs of the rural patients, particularly in the immediate aftermath of the merger
(American Health Information Management Association, 2012)
Over 440,000 deaths were a result of PAEs in inpatient and outpatient U.S.
healthcare settings (James, 2013). Many of these PAEs were linked to the poor quality of
care. Rural U.S. citizens are 50% more likely to die from preventable causes, and
compared with urban populations, rural communities still experience a newborn death

rate 25% higher (Moy et al., 2017; Roth, Denney, Amiri, & Amram, 2019; U.S. NVSS,
2017). According to the U.S. Census Bureau (2016), unintentional PAEs such as drug
over-doses, increased chronic diseases and declined life expectancy, and the incidence of
diseases and morbidities are about 50% higher in rural areas than in urban cities. The
CDC (2017) and Harris et al. (2016) attributed this disparity to differences in
socioeconomics, health behaviors, and access to health services. These disparities have
even become more apparent when examining PSRs and CCDs due to hospital mergers
and acquisitions that have reached record-high spending.
Previous studies have shown some anticipated benefits of mergers, such as
improved financial performance, service consolidation, and operating efficiencies (Noles
et al., 2015). Various researchers have suggested mergers as an effective strategy for rural
hospitals in financial distress (Burkey et al., 2017). However, there has been a little
examination of the CCDs and PSRs that hospital mergers and acquisitions have on rural
patients. Declining reimbursement levels, increasing capital needs, a weak economy, and
easier access to credit have all attributed to a level of RHMs not seen in more than 2
decades (see Hass et al., 2018; Noles et al., 2015). To better understand the ramifications
of mergers and acquisitions for RHs, I developed the following four research questions to
guide this study:
RQ1: Is there an association of healthcare transformation changes in structures,
processes, organizational culture and values on clinical outcomes for rural
patients?

RQ2: What is the relationship between governance mechanisms and patient
outcomes in RHMs?
RQ3: How do best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and the
process of care?
RQ4: What is the relationship between clinician leadership and the quality of care
outcomes in RHMs?
To date, while many studies have focused on the association between hospital
consolidation and the financial aspects, no research has been conducted to explore or
identify specific areas where system complexities slow or inhibit the adaption of a
holistic patient safety culture in RHMs. Given the scale levels of need in rural
communities and despite the benefits of hospital mergers, patient care and safety must be
of great importance both during and after the transition planning phases (Noles et al.,
2015). To bridge this gap in the literature, I focused on four aspects of leveraging
organizational synergies in this study: change management, governance mechanisms,
system integration best practices, and the role of clinical leadership. Understanding the
relationship between hospital mortality and the potential performance comparisons of
rural hospitals post mergers could prompt policymakers to identify opportunities for
future quality improvement efforts that narrow identified gaps. The study results may
provide decision-makers with system-level indicators of quality and assist them in
exploring strategies that can be used to improve organizational performance.

The objective of section 2 was to present the research strategies and methods
related to data collection and analysis. In this section, I discussed the relevant theory and
the problem that has stimulated this study. My study was to identify an in-depth process
that can be used to articulate a definite need for a quality improvement initiative to ensure
the level of readiness and adaptability necessary for quality patient safety and provide a
useful outlet for minimizing CCDs. Network development leaders need to be aware of the
merging processes and best integration practices that will have positive influences on
reducing CCDs and PSRs. In this section, I provided the process of data collection
method from all relevant sources to find solutions to the research problem, test the
hypotheses and evaluate the outcomes. My aim was to present a thorough literature
analysis regarding the relationship between the following organizational synergy
complexities: governance mechanisms, hospital structures-care processes, clinical
leadership, and system integration best practices, and quality domains (i.e., CCDs and
PSRs) post mergers.
Research Design and Rationale
With the significant expansion of hospital mergers and acquisitions, there is a
problem with the quality, efficiency, and patient safety in the U.S. rural healthcare
delivery services, mainly related to RHMs (CDC, 2017; NC RHRRC, 2014; Unger et al.,
2018). Understanding the fundamental problem of quality of care in the disintegrating
healthcare system, which may result from integrating two independent facilities with
different values, is an essential first step to define the root cause of PAEs in RHs post
mergers. Such brokenness and unbalance due to systemic integrating misalignment,
competing interests, cultural differences, and inefficient allocation of resources, are at the

heart of the ineffectiveness of hospital processes, poor quality, and health inequalities. In
this study, I used a conceptual model to critically analyze gaps in healthcare quality in
RHMs, with the intent of systematically understanding the discrete components of quality
gaps and their potential mechanisms. Identifying specific areas of healthcare quality
problems in U.S. rural communities would provide actionable targets for future research
and quality improvement.
In this study, I applied a synthetical correlation conceptual approach that is
outlined by Donabedian’s vision for the evaluation of quality outcomes, which identifies
elements influencing care quality into structures, processes, and results, and furnishes a
theoretical perspective for research and interventions in quality improvement. This
approach was appropriate for developing and determining meaningful metrics to assess if
an association exists between organizational synergy complexities: governance
mechanisms, hospital structures-care processes, clinical leadership, and system
integration best practices and quality domains (i.e., CCDs and PSRs) post mergers. In this
study, I used the independent variable (i.e., RHMs) and the two dependent variables (i.e.,
CCDs and PSRs) to discern the relationship between rural communities and hospital
mortality through conducting a performance comparison of RHs post mergers.
Methodology -Theoretical Framework
In this study, I discussed some of the literature on the conceptual framework and
related metrics, either directly or potentially relevant to PSRs and CCDs in RHs post
mergers. This discussion was to provide a brief explanation of the selected potentially
useful framework and to demonstrate how the Donabedian’s quality improvement model

might be used to guide the development of this study. Thus, the purpose of this section 2
was to show that a theoretical perspective from this model could be applied to modify
structures and processes within healthcare delivery systems, such as integrating
organizations, to improve patient safety, information exchange, and minimize CCDs
(Ayanian et al., 2016).
In this study, I applied the Donabedian’s structure-process-outcome approach to
effect further improvement in hospital mergers and conduct a performance comparison of
RHs post mergers. The theoretical base for this study was the Donabedian’s quality
improvement model. Donabedian's three components approach for evaluating the quality
of care underpins the measurement of improvement initiatives. In this theory, Donabedian
(1988) explained that information about the quality of care could be drawn from three
categories-structure, process, and outcomes. Donabedian (2003) noted that each of the
three domains has advantages and disadvantages that necessitate researchers to draw
connections between them to create a chain of influence that is theoretically useful for
determining systems as well as designing experiments and interventions. This quality of
care model was developed to be blendable for care systems in disparate healthcare
environments and among various levels within a delivery system (Ayanian et al., 2016).
Donabedian further asserted that this theory could also be utilized to a sizeable healthcare
organization to evaluate the overall quality and align improvement programs across a care
system to improve quality and outcomes for a population.
Integrating healthcare organizations have inherent complex organizational
structures because of transformational changes in leadership, clinical care setting,

workforce challenges, changing patient expectations and demands, fiscal constraints,
increasing requirements for access to care, a mandate to improve patient-centered care,
and issues concerned with levels of quality and safety of health care (Daly, Jackson,
Mannix, Davidson, & Hutchinson, 2014). In addition to CCDs, health systems may deal
with complexity through various organizational structures such as decentralization,
centralization, or multiple channels of authority (Ayanian et al., 2016). Donabedian’s
conceptual model provided me with a practical framework for a research agenda that
could ultimately assess whether rural patients receive a lower quality of care and have
worse outcomes post mergers.
Because the theory describes that structure measures influence process measures,
which, in turn, affect outcome measures, the Donabedian’s quality improvement model
continues to serve as a touchstone framework in health services research in understanding
the actual effectiveness of new strategies or modifications within the care process (Moore
et al., 2015). Per the Donabedian (2005) model, it is critical for any improvement
initiative to have outcome measures, process measures, and structure measures, these
different types of actions have a unique objective in establishing whether the
improvement task has had the desired outcome. As the analysis of the methodologies of
this study, I focused on four dimensions of leveraging organizational synergies: change
management, governance mechanisms, system integration best practices, and the role of
clinical leadership to establish or evaluate the possible relationship between quality
domains.

Change Management Complexities
Various health care organizations, in the name of merging and consolidation, have
acquired a collection of overlapping practices that fail to achieve the intended goal of
safety system development (see Jennings et al., 2008). Previous researchers have
described the U.S. rural healthcare system as vulnerable, in part because of a confluence
of integrating health systems, each with seemingly competing interests, perspectives,
missions, values, and contrasting cultures (Noles et al., 2015). Among the evolving
hospital paradigm due to hospital mergers and a turbulent economy, the future for RHs
seems uncertain. As rural hospitals respond to increasing pressures of financial
constraints, they are opting to consolidate both diagonally and vertically to be able to
deliver integrated, cost-effective care; however, such shifts presents challenges for rural
hospitals, which often serve as the foundation for health care delivery in rural
communities and yet battle to conquer the ramifications of troubled economies, shortages
of health professionals, and public policy inequities (Moscovice & Stensland, 2002).
Unless merging organizations make a substantial long-term commitment to
changes in addressing the progressive deficiency that has been encountered by the
acquired health system, addressing the issue of quality of care, and managing
transformation can be challenging (see Baker, Denis, Pomey, & MacIntosh-Murray,
2010). Failure to cultivate an environment conducive to change and overcoming
resistance may lead to ever-increasing health disparities between rural and urban
communities (Cossman et al., 2017; Noles et al, 2015).

Governance Mechanism Capabilities
The future of organizational sustainment in hospital mergers requires highly
effective governance processes to confront a profusion of risks, including regulatory and
policy changes, performance, ethics, and quality of care issues. According to Baker et
al.2010, adopting a greater responsibility for quality and safety performance is
challenging for many boards and yet efforts to engage boards in improving care are based
on the rationale partnership to achieve economies of scale rather than patient-centered
care. Research suggests different cultures between integrating organizations will present
additional challenges with the balance of power resistance, goals misalignment, and an
array of clinical disruptions (Hass et al., 2018). However, overcoming such challenges
requires effective governance and heroic leadership, which is focused on generic based
quality and safety good practices. Donabedian conceptual model, therefore, has a
profound effect on helping hospitals to identify specific areas for clinical improvement
and created an environment that is conducive to improving the quality and safety of care.
System Integration Best Practices measures.
Healthcare is a sophisticated-adaptive system where interactions and relationships
of different components simultaneously transform and are shaped by nonefficient
integrated operations (Tsasis, Evans, & Owen, 2012). Intrinsically, it is critical for
performance initiatives to be integrated within the healthcare organization’s strategic
objectives post a merger. Key intentions, such as consolidating resources for efficiency,
expanding access points, boosting financial viability and market presence, focusing on
population health management, acquiring facilities for expansion, all require performance

improvement to be successful. Given the magnitude of barriers to implementing best
practices in RHMS, from cultural, clinical to financial, care institutions are confronted
with the challenge of identifying and creatively overcoming them to achieve and sustain
patient safety environments.
With confounding and inherent structure complexities emanating from nonbinding
long-term commitments to such an arrangement, participating hospitals are
understandably reluctant to exit from a service line (see Noether, & May, 2017).
Although implementing standardized tools such as decentralization, centralization, or
multiple channels of authority are not the quick fixes, the Donabedian’s quality
improvement model provides a vital framework of how change management complexities
may impact the adoption of a safety culture. Designing a quality safety culture model that
supports superior performance in terms of quality and safety as a result of effective
communication-best practices and standardized protocols in a manner that accomplishes
the hospital's needs is critical to significantly improving clinical, financial, and patient
outcomes.
Clinicians Leadership Roles
Research reveals that today’s leaders are hard confronted with multiple complex
issues that impact the ability to successfully implement cost-effective programs, maintain
efficient operations and services, and support patient safety initiatives (Daly et al., 2014).
Hass et al. (2018) argued that workforce challenges, changing consumer expectations and
demands, fiscal constraints, increasing requirements for access to care, a mandate to
improve patient-centered care, and issues concerned with levels of quality and safety of

health care all remain at the center stage of hospital mergers. With so many changes and
the sheer scale of competing priorities in RHMs, effective governance is imperative in
ensuring a high-quality health care system that consistently provides safe and effective
patient care.
In addition to deficiencies associated with condensed resources and demand in
rural hospitals, episodes of the prevalence of mortalities, cultures of poor care, and a
range of workplace difficulties have been associated with poor clinical leadership, and
these concerns have provided the impetus to evaluate clinical leadership roles more
carefully. Integrating hospitals and care systems in rural communities must adopt a
quality model that position structures, processes, and teams that support evidenced best
practices (Austin, Bentkover, & Chait, 2016). The pressure for managing these
responsibilities in striving for efficiency, control the costs and outcomes for an entire
episode of care, and sustainability is neither simple nor easy because it requires greater
adaptability in transformative change for the demands of a transforming healthcare
system (Kaufman et al., 2016).
In the changing environment where health systems need to audit their practices,
procedures, and facility cultures carefully during and after a merger to ensure that staff is
adequately prepared and trained for new challenges, the Donabedian’s quality model may
shed some light on the goals and responsibility for safety and quality which are usually
unclear. Consequently, recent research coupled with well-publicized patient safety
initiatives suggests that the Donabedian framework remains the dominant paradigm for
assessing and drawing inferences about the quality of care in a given system (Gardner,

Gardner, & O'Connell, 2013). Engaging clinicians during a merger and collaborating with
clinician leadership to drive best merging practices adoption post an alliance needs to be
thoroughly ingrained in hospital practices—to result in implementing a clear
accountability safety framework and relationships between all stakeholders.
Participants/Sample Size
Data Sources/Study Setting
Three hundred eighty hospital mergers during the period of 2010–2018 were
identified, and a random sample of pairs of rural hospitals that have merged or acquired
was drawn to establish a statistically efficient control cohort. Data used for the inquiry
were extracted from scholarly databases that track the mergers in RHs in U.S. citizens
from 2010 through 2018. RHs in U.S. rural counties nationwide during the period 2010 to
2018 was the focus of the study. The sources utilized consist of databases such as NC
RHRPRC publications, the health care services acquisition report produced by Irving
Levin Associates (ILAs), the Journal of Patient Safety, and the Journal of American
Medical Association, CDC and U.S. Census Bureau publications, Google Scholar and
Walden University’s library databases (see Neprash, Chernew, & McWilliams, 2017).
For triangulation in this correlation research, I used patient outcome measures of
mortality and readmission rate to study the effects of mergers on hospital quality of care
from the Hospital Compare website at Data. Medicare.gov.
Table 1.
Rural Hospital Mergers Ranked by State: Between 2010 and 2018
States
Mergers
States
Mergers

Oklahoma 36 Louisiana 7
Texas
Tennessee
Wisconsin
North Carolina
24
20
19
18
Oregon
Maine
Iowa
West Virginia
6
5
5
4
Pennsylvania 17 Kansas 3
Virginia
Georgia
South Carolina
Alabama
Illinois
Michigan
Ohio
Arkansas
Missouri
New York
Mississippi
Kentucky
Minnesota
Indiana
Florida
16
16
15
14
13
13
12
11
11
11
11
10
10
9
9
California
Connecticut
Maryland
Nebraska
South Dakota
North Dakota
Arizona
Montana
New Mexico
Washington
New Hampshir
Hawaii
Nevada
Idaho
Massachusetts
3
3
3
3
3
3
2
2
2
2
1
1
1
1
1
From “Rural Hospital Sustainability Index Data,” by Navigant, 2019
(http://www.navigant.com/navigant.com)
Table 2 shows that, on average, over 400 U.S. rural hospitals are vulnerable or are
at a 20% risk for closure or a merger. The risk of closure due to the financial crisis,
potentially hinder many U.S. rural citizens' access to care. Overall, data presented on this
table support that the risk for rural hospitals closures or mergers in U.S. states run from
lower 3.6% to 50% high (see Mosley & DeBehnke, 2019).
Table 2.
Number of Rural Hospitals that are At Risk to Merge/Close by State
States
Oklahoma 58 17 23.9
Total RHs
RHs at Risk
% at Risk

Texas 21 1 4.8
Tennessee 37 7 18.9
Wisconsin 95 17 17.9
North Carolina 15 4 26.6
Pennsylvania 41 9 22.0
Virginia 27 10 37.0
Georgia 22 1 4.5
South Carolina 63 26 41.3
Alabama 42 21 50.0
Illinois 75 9 12.0
Michigan 71 18 25.4
Ohio 65 7 10.8
Arkansas 49 18 36.7
Missouri 61 14 23.0
New York 48 9 18.8
Kentucky 65 16 24.6
Mississippi 64 31 48.8
Minnesota 89 19 23.1
Indiana 10 1 10.0
Florida 13 0 0.00
Oregon 28 1 3.6
Maine 40 8 40.0
Iowa 17 0 0.0
California 50 4 8.0
West Virginia 37 7 18.9
Kansas 101 29 28.7
Utah 127 12 9.4
Maryland 5 0 0.0
Nebraska 70 8 11.4
Washington 23 8 34.8
Idaho 40 6 15.0
Vermont 39 9 23.1
Wyoming 25 3 12.0
New Hampshire 17 5 29.4
Note. 19% of the U.S. population is served with rural hospitals at high operational risk.
Top risk States show a 20% or more and represent the vulnerability of communities.
Sampling and Sampling Procedures
Rural hospitals that have merged or acquired between 2010 and 2018 were the
target population for this research study. Three hundred and eighty mergers involving
rural hospitals from 2010 through 2018 were identified from the Health Care Services
Acquisition Report produced by ILAs. The Hospital Compare datasets, updated
periodically on the Medicare.gov Hospital Compare Website provided by the CMS, was
utilized to analyze and to pinpoint the impact of acquisition-driven transformational

changes on the quality performance of acquired rural hospitals. Based on the data
source’s capabilities in enabling researchers to compare the quality of care at over 4,000
Medicare-certified hospitals across the country, this data source was significant to the
study.
As highlighted in the previous section, this correlational study utilized archived
and secondary data from the Hospital Compare website at Data. Medicare.gov. The
literature review was comprised of journals and articles from the NC RHRPRC
publications, the Journal of Patient Safety, and the Journal of Medical Association, AHA,
CDC and U.S. Census Bureau publications, Google Scholar, and Walden University’s
library databases. Procedures for data collection was composed of transferring data in
Microsoft Excel tables, and data analysis was performed through IBM SPSS Statistics
Version 25.
Power Analysis
Power analysis using G*Power 3.1.9.4 was performed to ascertain whether the
number of hospitals incorporated in the study would be appropriate to detect a significant
correlation at a small effect size of (Z = 02). Considering the logistic regression with an
alpha set at 0.5, effect size of .15 with a 1.4 odds ratio and 80% predictive power, the
minimum number of hospitals included in the study was 348, as shown in Figure 1. In
this case, the predictive power of 80% was selected to determine the minimum lower
level of sample size. However, a final sample size of 380 rural hospitals that have merged
or acquired was analyzed to find if there is a compelling association that exists in the
population.
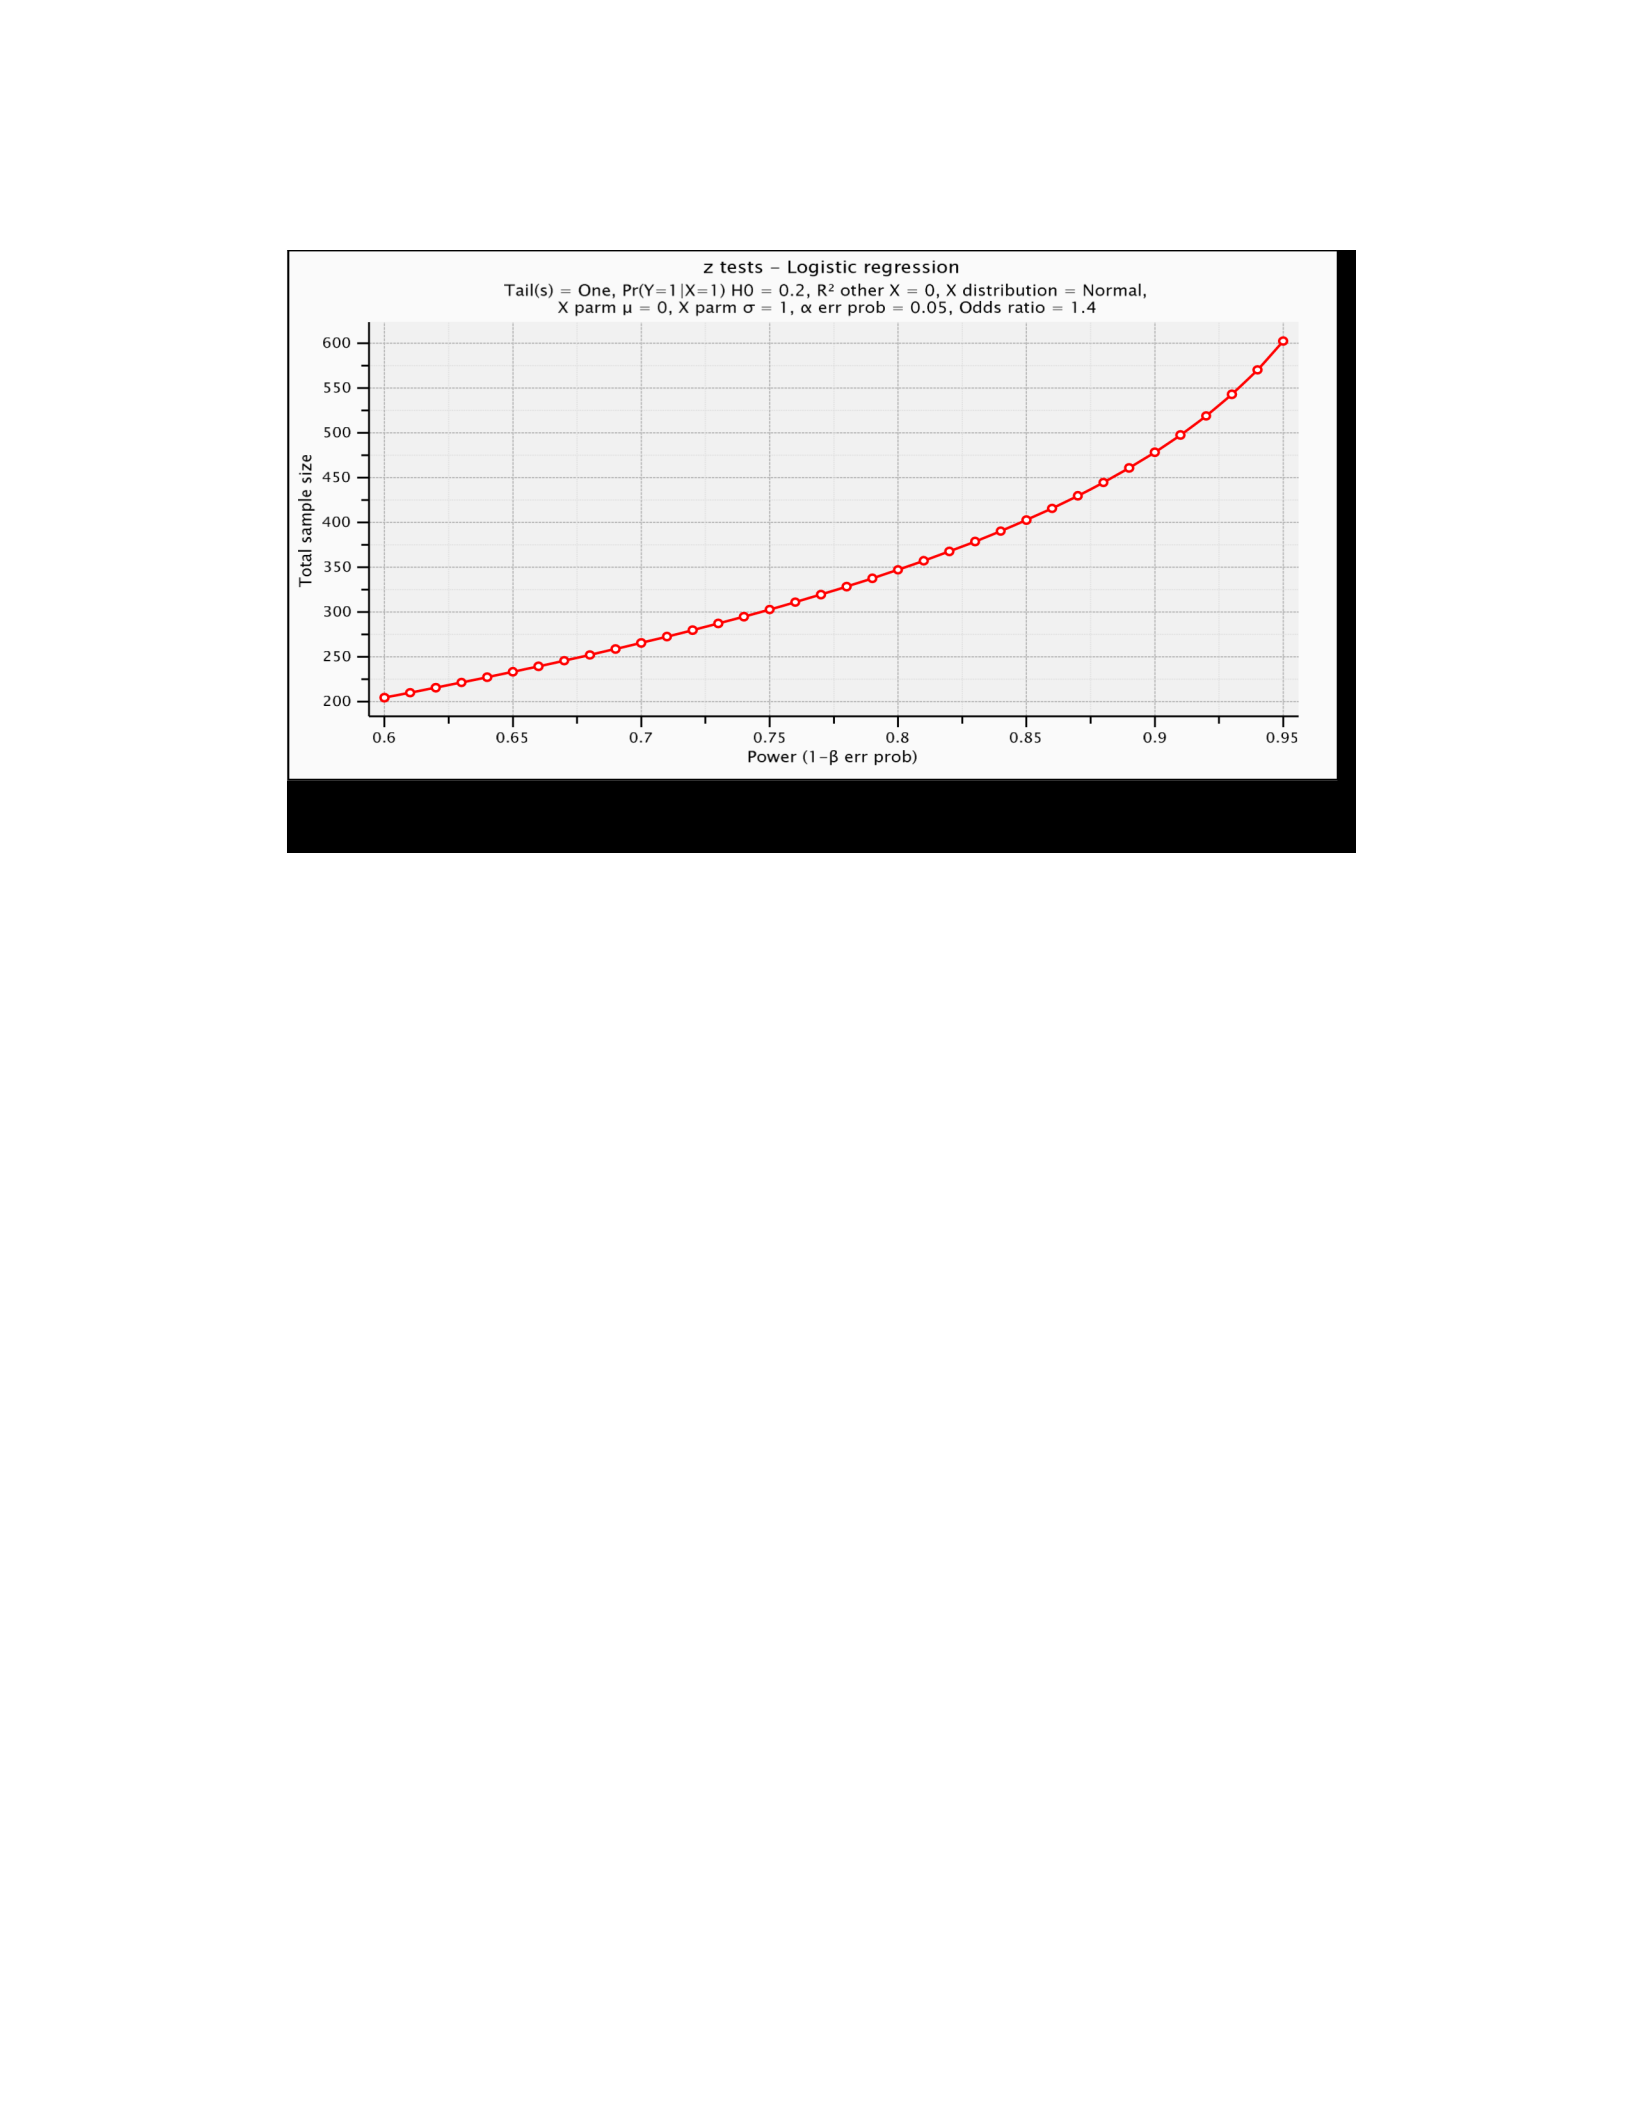
regression analysis priori function as represented in the graph
Data Collection, Strategy, and Management
Keywords such as patient risks, clinical care disruptions, organization structural
changes, organizational complexities, hospital mortalities, and rural hospital mergers
were utilized to assist in finding and locating relevant literature of this study. The library
sources searched include journals and articles from the NC RHRPRC publications, the
Journal of Patient Safety, and the Journal of Medical Association, AHA, CDC and U.S.
Census Bureau publications, Google Scholar, and Walden University’s library databases.
The literature search of my study explored to precisely assess the performance of rural
hospital alliances regarding structures, processes, and outcomes and evaluate the
correlation between quality domains. In this correlation research, I used patient outcome
measures of mortality and readmission rate to study the effects of mergers on hospital
quality of care.

This quantitative study exploited data from publicly available Medicare Mortality
Ratings Databases, Hospital Compare, and Hospital Evaluation Databases (2010–2018)
to research the performance differences. In addition to the analysis, data from scholarly
databases that track the mergers in rural hospitals in all 50 U.S. states within the period of
2010–2018 were extracted. These secondary datasets are available to the public, and the
data is de-identified with no personal identification to any patients. An authorization for
research to access the data was obtained from the Walden University Institutional Review
Board with an approval code of 07-18-19-0496865.
Instrumentation and Operationalization of Constructs
To better study the quality of care, level of clinical care disruptions, and
understand the mechanisms accounting for any potential performance differences in care
for rural patients post mergers, Donabedian (2005) conceptual model for Assessing
Quality of Care was exploited. This model was deployed to establish whether a structure
(organization structural changes in RHMs) and processes (hospital performance) are
associated with quality outcomes or may ultimately lead to increased PSRs (PAEs,
mortality, morbidity, rehospitalization rates, and clinical care disruptions). Other IOM
quality domains such as timely, effectiveness, equity, efficiency, safety, and
patientcenteredness care measures were considered to strengthen the model of the study
(AHRQ, 2016).
The statistical research tool that was appropriate to analyze data of this
quantitative study was IBM SPSS Statistics 25. Data collected from both the secondary
documents and from the Data.Medicare.gov was entered into SPSS computer software

and analyzed to answer research questions, test hypotheses, or disprove theories. As
outlined in the Donabedian’s quality improvement model that outcomes refer to the
effects of healthcare on the health status of patients and populations, I proposed that the
construct for this study to be model driven on patient safety culture.
Operationalization
This model strives to elucidate how specific organization structural complexities
inherent in hospital alliances and in providing care to rural patients can affect processes
and lead to poor outcomes. The study needed to display whether such relationships
between transformational changes and PSRs and CCDs post-RHMs does exist. According
to the Joint Commission’s Patient Safety Systems Chapter, patient safety culture is the
value of what a hospital is and how it does surpass its safety targets (Joint Commission,
2016). Evaluating and assessing the PSRs and CCDs of health care is critical because it
reflects how the institution is performing and leads to improved care post-mergers.
Emanuel et al. (2008) interpreted patient safety as a characteristic of health care systems
that reduce the incidence and prevalence of death and the impact of preventable events
and maximize recovery from such activities.
Because patient safety demands the design of systems in integrating organizations
to make risky interventions reliable and which cannot be directly detected, an attempt to
assess risk effect by operationalizing PSR variables (mortality rates, morbidity, hospital
readmissions, and PAEs) was made. Variables analyzed were identified and scaled in
numeric, and these include RHMs (independent variable) and PSRs and CCDs
(dependent variables). Understanding the relative strengths of the proposed model

components and tested association of measurement methods discussed here could help
investigators, clinicians, administrators, and policymakers meet this goal.
Table 3.
Dependent and Independent Variables
Dependent (PSRs and CCDs) Independent Covariates
Mortality rates
Hospital readmissions
Morbidity level
PAEs
Rural hospital
that have merged
or acquired
(RHMs)
Hospital
performance
merits (urban vs
rural hospitals)
Timeliness of
care
Safety of care
Patient
experience
Financial ratio
Data Analysis Plan
To summarize the collected information for interpretation, answer my four
research questions and presentation of the findings, the data collected from the secondary
documents were entered into SPSS computer software and analyzed as considered
appropriate. The specific variables investigated were RHMs (independent variables) and
patient risks and CCDs (dependent variables). Models constructed from hypotheses
concerning health systems and patient safety risks and clinical care turbulence pertinent
to the likelihood of a merger were tested using logistics regression analysis.
The technique allowed this study to determine the relationship between
organizational systems and the level of CCDs and the prevalence of PSRs after mergers.
The purpose of utilizing this analytical sampling technique was to determine if

statistically significant correlations exist between the two dependent variables (PSRs and
CCDs) and the independent variable (RHMs) while adjusting for each covariate of
organizational complexities (hospital care process, clinical care leadership, governance
mechanisms and system integration best practice indicators). Key findings and study
results will be presented in section 3. A total of four research questions were examined to
determine the association between organizational synergy complexities and CCDs and
PSRs in RHMs:
Research Questions and Hypotheses
RQ 1: Is there an association of healthcare transformation changes in structures,
processes, organizational culture, and values on clinical outcomes for rural
patients?
H01—There is no association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical
outcomes for rural patients.
Ha1—There is an association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical
outcomes for rural patients.
RQ2: What is the relationship between governance mechanisms and patient
outcomes in RHMs?
H02—There is no relationship between governance mechanisms and
patient outcomes in RHMs.

Ha2—There is a relationship between governance mechanisms and patient
outcomes in RHMs.
RQ3: How do best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and the
process of care?
H03—Best practices do not facilitate quality-focused initiatives and do not
contribute to eliminating unintended patient risks associated with
structural changes and the process of care.
Ha3—Best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and
the process of care.
RQ4: What is the relationship between clinician leadership and the quality of care
outcomes in RHMs?
H04— Clinical leadership in RHM and acquisition deals is not a
significant predictor of quality of care outcomes.
Ha4—Clinical leadership in rural RHM and acquisition deals has a
significant relationship with the quality of care outcomes.
Threats to Internal and External Validity
Challenges about secondary use of data mostly emerge around potential harm to
individual subjects and the issue of obtaining consent (Tripathy, 2013). However, in this
study, there were very few threats to the internal and external validity of data. As
previously highlighted in the data collection strategy section, the data contained in the

Hospital Compare at CMS.gov is a public-use secondary dataset that is patient
deidentified. In addition to secondary data analyses serving in this study as an economical
alternative to an expensive and time-consuming data collection process, most research
projects that consist entirely of secondary data analysis raise few ethical considerations
(Boo & Froelicher, 2013). There is the only area of concern to the reliability and validity
of datasets used in the secondary analysis that mostly emanate from the precision and
integrity of the techniques of data collection used in the initial data collection process.
Ethical Procedures
For ethical purposes, an authorization for research to access the data was obtained
from the Walden University Institutional Review Board with an approval code of 07-
1819-0496865. To maintain the security of the datasets, data for this study were
downloaded and stored in a password-protected archival file and deleted after the
investigation. To keep the threats of ethical issues at minimal, the Walden Institutional
Review Board supervised the collection of data and ensure that this research study
complies with all the university's ethical standards as well as U.S. federal regulations.
Summary and Positive Social Change Implications
Evaluating the quality of health care and promoting a culture of safety is crucial
because it reveals how the healthcare organization is performing and leads to improved
care. To better understand the impact of mergers and acquisitions for rural hospitals on
quality performance, this brief examined four research questions.
With hospital mergers on the rise, organizations that invest in building active
patient safety cultures stand to benefit. Understanding and properly implementing quality

initiative, is essential to a well-functioning health system and is necessary for any practice
interested in improving performance, patient safety, or clinical outcomes. In addition to
identifying opportunities for quality improvement. and foster a commitment to
excellence, a measure that carries substantial weight, as well as necessary implications
about safety of care, is a hospital's mortality rate. Through the study results, I hope to
support this commitment by helping health care leaders understand how reducing hospital
mortality rates and eliminating PAEs can improve health care safety and the quality of
care delivered to rural patients. While PSRs and CCDs in the U.S. rural hospital delivery
services may vary widely when calculated systematically and categorized according to
the level and type of care, patterns emerge that can highlight system defects. Although
several studies have documented the need for U.S. hospitals to reduce inpatient mortality
rates and PAEs, there is a scarcity of literature on effective methods to accomplish this
goal. Therefore, this research study adds to the knowledge needed for policymakers to
make decisions and establish a nationwide systematic process and develop a stronger
culture of continuous quality improvement in RHMs.
In Section 2, I documented and presented the quantitative processes necessary to
complete this correlational study. The conceptual framework of this study, study sample,
and sampling procedures, including instrumentation, operationalization of constructs, and
data collection strategy and management, were outlined and thoroughly discussed. In
addition to the restating of research questions, data analysis plan, and the purpose of
research design and how it could present meaningful results to the stakeholders of the
industry was proposed. This section concludes with highlighting threats to internal and

external validity, along with ethical concerns and procedures. My study results and
findings will be discussed and interpreted in Section 3.

Section 3: Presentation of the Results and Findings
Introduction
The principal goal of this study was to examine the potential association of
healthcare transformation changes in structures, processes, organizational culture, and
values on clinical outcomes for rural patients post mergers. A secondary intent of the
research was to enhance the understanding of the incidence of patient risks and clinical
turbulence in RHMs as a basis to reduce them. Periodic exposure of potentially PAEs in
rural communities might help public health departments identify emerging health
problems, monitor known issues, and focus interventions on reducing excess mortalities
in these areas (Moy et., 2017). In this correlational study, I focused on four aspects of
organizational synergies: governance mechanism capabilities, change management
complexities, clinical leadership, and system integration best practices. The governance
mechanisms (i.e., controls, policies, and guidelines), hospital structures i.e., (care
processes), clinical leadership (i.e., management cultures), and system integration best
practices were examined to determine their relationship to the prevalence of clinical care
turbulence and patient risks. Recent literature supports possible negative consequences
from mergers and acquisitions, although not conclusively (see Hass et al., 2018),
however, the potential health effects of mergers have received less attention in the
literature than other significant organizational changes, such as health care profitability
and cost cutbacks.
In this study, I employed the quantitative approach to describe PSRs and CCDs in

RHMs. In this research study, I accurately assessed and examined the performance of
rural hospital alliances regarding structures, processes, and outcomes and evaluated the
correlation between quality domains. I aspired to present an upgraded awareness of the
strategies harnessed by developmental leaders in integrating processes to safeguard rural
communities and promote a culture of safety excellence. In section 3, I discuss the data
collection methods, data selection criteria, data analysis methodologies, and a summary
of the analytical results.
The potential clinical consequences, PSRs, and outcome quality measures were
the dependent variables. Different structural factors and organizational synergies
consisting of new settings for providers, uncharacteristic system integration practices,
institutional relationships, governance mechanisms, and new patient populations served
as co-variables potentially associated with process and outcome measures. The RHMs
and the facility characteristics were the independent variables. A benchmark evaluation of
strategic controls, financial measures, and operating performances, as well as gaps and
regulatory requirements, were also included in the study as covariates because the
attributes are related to hospital quality performance competencies. (see Haas et al.,
2018). To further understand the areas of risks in RHMs, I utilized these structureprocess-
outcome independent and dependent variables to address the following research questions
and associated hypotheses.
RQ 1: Is there an association of healthcare transformation changes in structures,
processes, organizational culture, and values on clinical outcomes for rural
patients?

H01—There is no association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical
outcomes for rural patients.
Ha1—There is an association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical
outcomes for rural patients.
RQ2: What is the relationship between governance mechanisms and patient
outcomes in rural RHMs?
H02—There is no relationship between governance mechanisms and
patient outcomes in RHMs.
Ha2—There is a relationship between governance mechanisms and patient
outcomes in RHMs.
RQ3: How do best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and the
process of care?
H03—Best practices do not facilitate quality-focused initiatives and do not
contribute to eliminating unintended patient risks associated with
structural changes and the process of care.
Ha3—Best practices facilitate quality-focused initiatives and contribute to
eliminating unintended patient risks associated with structural changes and
the process of care.

RQ4: What is the relationship between clinician leadership and the quality of care
outcomes in RHMs?
H04— Clinical leadership in RHM and acquisition deals is not a
significant predictor of quality of care outcomes.
Ha4—Clinical leadership in RHM and acquisition deals has a significant
relationship with the quality of care outcomes.
In section 3, I discuss and present the core findings of this study as derived from
the methods applied in gathering and analyzing the research data. In this section, I
describe the data analysis and offer a summary of the answers to the research questions.
An overview of the time frame, response rates, discrepancies of the data set with baseline
descriptive logistic regression analysis, and demographic characteristics of the sample
were also provided.
Data Collection of Secondary Data Set
To examine differences in performances of rural hospitals that have gone through
mergers or acquisitions, I analyzed mortality data for U.S. rural residents from the NVSS
and readmission hospital data from Hospital Compare Datasets throughout 2010 to 2018
(see Mack, Jones, & Ballesteros, 2017). The NC RHPRRC center that performs
fundamental research in rural health care delivery matters and provides in-depth policy
analysis to address social issues affecting rural populations, defined and characterized
rural hospitals as facilities positioned in a non-metropolitan community (Health
Resources and Services Administration, 2018). Utilizing data from NC RHRPRC and

ILAs' Healthcare Mergers & Acquisitions reports collected from 2010 through 2018, I
identified a total of 380 rural hospitals that have merged or been acquired. Both NC
RHRPRC and ILAs maintain a publicly available map for tracking and counting RHMs
and closures. ILAs is the commanding developer of business literature in the senior
housing and care and healthcare mergers and acquisitions markets, and it is the most
extensive database capturing all publicly announced healthcare mergers dating back to
1993 with more than 26,000 transactions in 13 healthcare sectors (see Noles et al., 2015;
Su, 2017).
I systemically evaluated hospital quality using metrics published in the Hospital
Compare database collected by the CMS. Given the outcomes of care provided by health
systems are of the most significant concern in the transformation to the evidence-based
safety care model, I primarily focused on structure, process, and outcome measures of
quality. In this study, I used routinely collected CMS outcome measures to calculate
overall hospital quality. Inconsistent with the 2018 CMS star rating report, outcome
measures were grouped into six categories weighted by importance: mortality, safety of
care, readmissions, patient experience, effectiveness of care, and timeliness of care. To
reduce the variability in these measures of quality, I combined the six separate outcome
measures tracked by CMS into three composite outcome indices: one for mortality, one
for readmission, and one that combined both mortality and readmission measures.
Regression Analysis Methodology
I performed a logistic regression analysis to determine hospital performance and
safety level characteristics that were correlated with the likelihood of transformation

changes in structures, processes, organizational culture, and values in RHMs. A streak of
multiple regression models was then utilized to establish if there were statistically
significant variances in key hospital quality predictive indicators (i.e., PSRs and CCDs)
post-mergers as compared to non-merged RHs. In this study, hospital factors, such as
hospital governance effectiveness, critical hospital access status, best practices for
hospital quality, clinical leadership, and hospital care systems were included to adjust
systematic differences between RHMs and non-merged hospitals.
I categorized the performed regression analyses to evaluate the relationship
between hospital performance safety measures into six quality indicators- mortality,
safety of care, readmissions, patient experience, effectiveness of care, and timeliness of
care. In these regression analyses, hospital organizational characteristics, such as hospital
size, urban/rural location, ownership type, and teaching status were used as controls for
factors that could influence this association and provide some specifics on whether the
impact of acquisition might vary over time.
Mortality 20%
o Cancer mortality rate o Heart failure and Stroke -the cerebrovascular diseases
mortality rate o Mortality rates for pneumonia (PN), Chronic lower respiratory
diseases
Hospital Readmissions 20%
o All causes readmission rate o PN and Influenza readmission rates o Heart
failure (HF) and Stroke readmission rates o Hip/knee replacement readmission
rate
Effectiveness of Care 20%
o Preventive care (includes influenza vaccination measures)
oCataract surgery outcome o Blood clot
prevention o Pregnancy and delivery care
Safety of Care Outcomes (Hospital Associated Events). 20%
o Adverse Events-Infections o Diagnostic errors o Medication errors o Surgical
complications
Timeliness of care 10%
o Heart attack (HA) care o Emergency department care
oPreventive care (includes influenza
vaccination measures) o Cancer care o Use
of medical imaging
Patient Experience 10%
o Focused on quality, patent-centeredness, satisfaction, and other concepts o
Patients rating services according to the quality of care they receive
Figure 2. Quality-safety performance measures weighted by importance
Financial and operational performance measures weighted by importance
Total profit margin
Percentage of equity financing
Medicare inpatient services
Medicare outpatient revenue/total revenue
Study Results
In this analysis, using metrics published in the Hospital Compare database
collected by CMS, I evaluated hospital performance relative to four common conditions
and procedures, offering insight on the variation in clinical quality and outcomes across
the country. My principal analysis included 380 RHM transactions and 4,964 control

hospitals (for a total of 5,344 hospitals). The total sample of the study (shown in table 4)
consisted of 19,671,254 hospital readmissions at 5,344 urban and rural hospitals across
50 states in the United States. Of that total 7,445,133 were readmissions in urban
hospitals, which accounted for 30.0% of the unplanned hospital readmissions (UHRs);
5,705,756 were in nonmerged hospitals, which accounted for 23.0% of the UHRs; and
11,655,365 were RHMs, which accounted for 47.0% of the UHRs respectively. A total of
380 (7.1%) were in RHMs, 2,569 (48.1%) were urban hospitals, and 2,395 (44.8%) were
nonmerged facilities. The overall rate of cancer characteristics for RHMs was 3.9%, with
a 1.8% difference (95% CI, 1.59% to 1.65%) compared to urban and nonmerged hospitals
(p < 0.01). Both the rate gap for heart diseases and pneumonia in RHMs were higher
39.0%; and lower 2.4%, with a -0.6% difference (95% CI, -0.7% to -0.5%) and
(95% CI, -0.8% to -0.6%) in comparison to urban and nonmerged hospitals (p < 0.01).
The common deficient pattern for overall UHRs in RHMs in patient characteristics was
observed as Black readmissions at 15.3% with a -8.6% difference (95%, -8.16% to 6.9%)
compared to urban and nonmerged hospitals (p < 001). In comparison to the White
population, between RHMs and nonmerged and urban hospitals on UHRs, both Hispanic
and non-Hispanic (other) had a negative -0.4% difference (95%, -0.4% to 0.23%) and
0.27% difference (95%, -0.2% to -0.3%) respectively at (P < .00). Inconsistent with
previous studies, the findings of the current study support the argument that RHMs are
associated with modest deterioration of patient experiences, compromised quality of care,
and significant changes in readmission rates. As seen in Table 4, the prevalence rate of
chronic obstructive pulmonary disease (COPD) shows a 36.6% increase in urban

hospitals, 2.5% lower for nonmerged hospitals, and 38.1% for RHMs, which is 1.5%
higher. These statistics support that the rural U.S. citizens experience higher rates of
UHRs and mortalities from COPD than residents living in more urban areas.
Table 4.
Comparison of Patient and Comorbidity Characteristics of Hospital Readmissions by
RHMs 2010-2018.
Characteristics
Urban hospitals
n=2569
Non-merged hospitals
n=2395
RHMs n=380 Difference CI 95%
Hospital Admissions
7,445,133 (30%)
5,705,756 (23%)
11,655,365 (47%)
Health issues Cancer
5.8
4.2
3.9
1.8(1.59 to 1.65)
Heart diseases 38.4 38.5 39.0 -0.6 (-0.7 to-0.5)
Pneumonia
COPD
Patient demographics
Age, Mean
SD/Y
Black
White
Hispanic
Other
3.6
36.6
80.2 (8.6)
59.2
8.1
85.2
2.1
2.5
2.5
2.5
79.1 (8.4)
58.3
10.2
86.1
1.8
2.3
2.4
38.1
78.3 (8.3)
57.1
15.3
78.6
1.9
2.2
-8.6 (-0.8 to-0.6)
0.81 (0.8 to 0.9)
1.27(1.26 to 1.29)
3.08(3.0 to 3.3)
-8.16(-8.3 to -6.9)
0.02(-0.02 to 0.03)
-0.4 (-0.4 to 0.23)
-0.27 (-0.2 to -0.3)
Note. A positive confidence of interval (CI) at 95%-small or lower significant association
of CCDs and PSRs on RHMs; a negative CI at 95%-higher or elevated association of the
effects of RHMs. COPD represents chronic obstructive pulmonary disease and SD/Y
represents standard deviation age per year
Table 5 depicts the examined Hospitals’30-day readmission rates for patients who
had initially been evaluated for the following conditions: HF, PN, coronary artery bypass
graft surgery, hip and knee replacement or chronic obstructive pulmonary disease. The
analysis compared each hospital’s reported readmission rate to national averages for each
of the conditions to determine hospital performances. Six hospital performance measures
which are consistently collected by CMS over the period: three measures of 30-day
readmission rates for acute HA, HF, and PN and three measures of 30-day mortality rates
for HA, HF, and PN were included in the study. To minimize the volatility in these
measures of quality, I combined the six separate outcome measures tracked by CMS into
three composite outcome indices: one for mortality, one for readmission, and one that
combines both mortality and readmission measures. The CMS evaluates these trends in
measure results over time to monitor patterns, changes, and potential unintended
consequences in the measurement results.
Table 5.
Multiple Regression Analysis for Changes in Performance Measure Composite Post
Merger for Acquired Hospitals as Compared with Control Hospitals 2010-2018
Variable Unstandardized Coefficients Standardized Coefficients
B S. E. Beta T factor Sig
Performance
quality measure
(National
Comparison)
Safety of care -.174 .033 -.156 -5.345 .000
Patient
experience
.538
.055 .372 9.804 .000
Effectiveness of
care
.086
.028 .104 3.120 .002
Readmissions .523 .024 .609 21.771 .000
Mortality .051 .041 .041 1.253 .209
Timeliness of
care
-.024 .028 -025 -851 .395
CCD Composite 29.325 .00 .00 .00 .66
PSR Composite 44.974 .00 .13 .00 .16
Performance
period
. 0.3
2010 4.465 0.5 0.2 12.6 0.4
2011 3.838 -0.4 -0.6 15.9 0.5
2012 3.806 0.8 0.4 23.1 0.1
2013 3.779 1.0 0.1 31.7 0.8
2014 4.132 -0.8 0.3 18.3 -0.9
2015 4391 0.00 0.4 0.615 0.6
2016 4.506 0.3 0.615 15.5 0.12
2017 3784 1.1 0.11 21.3 -0.4
2018 3.762 1.7 18.4 0.2
National
comparison of
hospitalization
Mortality
Rural 166.6 0.1 0.1 0.1 0.9
Urban 195.3 0.3 0.3 0.2 0.4
Note. Sig= Significance p < 0.01, t-factor two-tailed; CI = confidence interval 0.95%,
CCD = Clinical care disruptions composite, PSRs composite = Patient safety risks Table
6 highlights the number of rated and unrated rural hospitals by CMS quality performance
classification. Based on the usefulness of the quality star rating for comparing hospital
quality and possible ways to reduce the PSRs and CCDS, the study assessed up to 90
quality measures that cover seven domains (mortality, safety of care, readmission, patient
experience, effectiveness of care, timeliness of care and efficient use of medical
imaging). Significantly, 1,300 total hospitals, which account for 73%, were not rated. Of
the 85, which received a 5-star rating, only 27.1% of the rural hospital met the CMS
qualifications compared to the urban hospitals which received a 72.9%. The data
suggested that, on average, rural hospitals with weaker quality performance and elevated
PSRs were negatively associated with the likelihood of the merger process.
Table 6.
Comparison of CMS Star Rated Category Percentage Ratio of Rural and Urban
Hospitals in Each Quality Performance Classification 2017

Total No.
Hospitals
Rural Urban CMS Star Rating
1,782
85
939
1,763
668
107
1,300 (73.0) 23
(27.1)
418 (44.9) 846
(48.0)
167 (25.0)
17 (16.0)
482 (27.0)
62 (72.9)
517 (55.1)
917 (52.0)
501 (75.0)
90 (84.0)
Not Rated (Missing)
5*****
4****
3***
2**
1*
5,344 2,771 2,569
Note. From Hospital Compare Data archive, by CMS, 2017, U.S. Department of
Health
and Health Services, Baltimore,
MD.
(https://www.medicare.gov/hospitalcompare/Data/HCAHPS-Star-Ratings.html).
As seen in Table 7, the study analysis highlights the adjusted 30-day mortality
rates for each dependent variable stratified by hospital size. The more significant the
difference of each mortality rate among the sample of the hospitals, the higher the
chances of discovering statistical variabilities among the selected hospitals. Significant
variations were detected among RHMs, for-profit, and nonprofit hospitals. Among small
hospitals [ ≤ 99 Beds], the overall 30-day death rate was 9.9% of the total hospitalizations
for RHMs, 9.5% of the total hospitalizations for-profit hospitals, and 9.3% of the total
hospitalizations for for-profit hospitals with a 0.4% difference (95% CI, 0.1% to 0.7%).
For medium hospitals with bed count between 100 and 399, the overall 30-day death rate
was 8.6% of the total hospitalizations for RHMs, 9.3% of the total hospitalizations for
nonprofit hospitals, and 9.4% of the total hospitalizations for for-profit hospitals with a
0.8% difference (95% CI, 0.4% to 1.3%). Among the large hospitals with 400 bed count
or more, 9.3% was accounted for the overall 30-day death rate for RMHs, 8.9% was
accounted for the overall 3.-day death rate for nonprofit hospitals, and 9.1% was

accounted for profit hospitals with a 1.2% difference (95% CI, 0.9% to 1.5%) at p < 0.01,
and the outcome differences were statistically significant by RHMs for the overall
hospitalizations in this size category. Of the 380 RHMs compared to the 3,664 for-profit
and 1,300 nonprofit hospitals, there were modest differences in both surgical procedures
and all medical conditions.
Differences in the structure and process of care between RHMs (for-profit and
nonprofit) and urban (nonprofit and for-profit) hospitals may also be a cause for the
increased morbidity rates in RHMs. Typically, rural hospitals face unique challenges
compared to other, more extensive facilities, with most pressing issues of coordinating
and managing care. High volume patient turnover, workforce shortages, and an aging
infrastructure that institution stakeholders do not always have the resources to update.
Besides, rural hospitals are often geographically isolated, which further limits these
health systems easy access to resources. These unique complex challenges of care and
continually changing processes of care and culture may create conditions in which
complications, particularly infections, occur more frequently. Hence, the increased
mortality and hospitalization rates observed in certain circumstances and operations in
RHMs in this study might be due to the characteristics of patients, and not necessarily
because mergers compromised the processes in the rural hospitals
Table 7.
Correlation of Between Adjusted 30-Day Hospital Readmissions and Rural Health
System Status by Health System Type 2010-20182010-2018
Total
admissions
Rural hospital
mergers n=380
For profit
hospital
n=3,664
Nonprofit
hospitals
n=1,300
Difference
(95% CI)
P value
Small hospitals
(≤99 Beds)

Cases
2,543,802 20,596,115 (9.9) 261,879 (9.5) 2,281,923 (9.3) 0.4 (0.1 to 0.7) .01
Comorbidity 1,462 201 860,064 (11.9 143,325 (11.3) 458,818 (7.8) 0.5 (0.1 to 0.9) .01
Surgical cases 77,779 36,050 (7.8) 9,605 (3.5) 32,144 (3.8) 0.3 (-0.1 to 0.7) .018
Medium hospitals
(100-399 Beds)
Cases
11,802,681
461,010 (8.6)
4,083,475 (9.3)
7,258,196 (9.4)
0.8 (0.4 to 1.3)
.003
Comorbidity 5,986,284 201,184 (11.3) 2,015,603
(11.8)
3,769,497
(11.8)
05 (0.04 to 1.0) .012
Surgical cases 496,611 20,614 (3.6) 182,446 (4.0) 293,551 (4.2) 0.6 (0.2 to 0.9) .011
Large hospitals
(≥400 Beds)
Cases
7,105,341
3,122,215 (9.3)
2,869,375 (8.9)
1,113,751 (9.1)
1.2 (0.9 to1.5)
.001
Comorbidity 3,171,715 1,276,866 (11.0) 1,348,310
(11.6)
546,539 (12.0) 1.0 (0.6 to1.4) .001
Surgical cases 334,814 144,976 (3.2) 140,154 (3.6) 49,684 (3.8) 0.7 (0.4 to 0.9) .001
Note. Standard errors. p < 0.01, p < 0.05, p < 0.1. A positive p-value indicates
statistically moderate/strong quality level association and a negative p-value signifies
weak association on performance quality level.
A Pearson regression (PC) coefficient analysis was conducted to determine the
correlation strength and direction between the continuous variables and the dependent
variable from the study sample (n = 5,344). Table 8 depicts the results of the PC
indicating a significant moderate positive relationship between all 30-day mortality
categorical and organizational synergies complexity characteristics. Hospital governance
effect (HGE) ratio (r = -733, p = .005); critical hospital access status (CHAS) ratio (r
= .238, p = .000); hospital integration best practice (HBP) ratio (r =.476, p = 0.01);
clinical leadership effect (CL) ratio (r = .430, p =.570), structural hospital care systems
(SHCS) ratio (r = .029, p = .0.01).The statistical analysis portrays the correlation of
hospital performance and safety level characteristics with the likelihood of transformation
changes in structures, processes, organizational culture, and values in RHMs.
Table 8.

Pearson Regression Coefficients of Organizational Synergies Complexity Between All
Categorical 30-Mortality Rate and Continuous Variables on RHMs
Source No. of Hospitals
(n)
R P
HGE (Hospital
Governance
Effect)
5,344
-.733
.005
CHAS (Critical
Hospital Access
Status)
5,344
.238
.130
HBP (Hospital
Integration Best
Practices)
5,344
.476
0.02
CL Ratio (Clinical
Leadership Effect
SHCS (Structural
Hospital Care
Systems)
5,344
5,344
.430
.029
.570
.0.01
Note. n=Total number of hospitals; r= Pearson correlation coefficient; Sig= Significance
p < 0.01, t-factor two-tailed.
In the analysis and based on the significance of the overall regression,
organizational synergies complexities (i.e., change management, governance
mechanisms, system integration best practices, and the clinical leadership) were assessed
to determine its impact on CCDs and PSRS due to RHMs. Statistical analysis, as shown
in Table 9, indicated that the effects of organizational complexities were significantly
predictive of changes in hospital performance (p < .001). The findings indicated that
much of the increase in the likelihood of transformation changes in structures, processes,
organizational culture, and values corresponded with the effect ratio of organizational
complexities. These results implicate not only patient care but ratings to rural hospitals,
which may be subject to the CMS unplanned readmission penalty for higher-
thanexpected 30-day readmission rates. Further, the findings from the study suggest that

hospital mergers may be related to impaired quality of care delivered at acquired
facilities, which fail to use performance indicators to support internal quality
management.
Table 9.
Logistic Regression Analysis of Organizational Synergies Complexity on Effectiveness
Hospital Integration (Merger Process)
Unstandardized
Coefficients
Standardized
Coefficients
B S.E. Beta t Sig
HGE ratio
-.029
.425
-.069
.945
HBP ratio .549 .034 .367 16.210 .000
SHCS ratio .373 .020 .089 18.460 .000
CHAS ratio .081 .024 .089 3.329 .001
CL ratio .024 -.079 .435 4.365 .002
Note. Dependent variables (mortality national comparison and hospital performance) were used in
the analysis.
Table 10 presents the results of the means for the calculated clinical quality and
safety scores, the predicted possible scores per CMS, the gaps, and the percentage gaps.
On average, 380 RHMs included in the study sample had a greater than 16.9% gap on
most of seven hospital performance and safety measures. Safety composite measure
highlights the highest average percentage gap of 42.65 on catheter-associated urinary
tract infection (CAUTI), followed by clinical care domain-PN 30-day mortality rate with
24.35%. Although, other the performance measure variables show lower percentage gaps
in both the clinical care domain (CCD) and safety domain scores (SDS), the predictors
were statistically significantly correlated to at least one organizational synergies
complexity (i.e., change management, governance mechanisms, system integration best
practices, and the clinical leadership) due to effects of RHMs.

Table 10.
Clinical Care Domain Estimates and Quality Gaps in Deaths by 30-Day Mortality and
Hospital Unplanned Readmissions Rate in RHMs.
Calculated score
identified (X*)
Mean S. E
Predicted score
(X**)
Mean S. E
Score difference
(X*-X**)
Mean S. E
Score gap %
Mean S. E
Clinical care
domain (CCD)
Acute myocardial
infarction (AMI)
30day mortality rate
11.09 1.65
10.64 0.56
0.45 1.09
4.06 13.74
Heart failure (HF)
30-day mortality
rate
11.56 1.96
9.78 0.61
1.78 1.35
15.40 14.76
Pneumonia (PN)
30day mortality rate
Safety domain
scores (SDS)
Surgical site
infection (SSI)
Catheter-associated
urinary tract
infection (CAUTI)
30 -Day Unplanned
Readmissions (PN)
30-Day Unplanned
Readmissions (HF)
1.15
0.75
0.68
25.09
19.35
0.28
0.08
0.15
2.39
1.83
0.87 0.03
0.65 0.03
0.39 0.06
23.93 1.05
16.68 0.69
0.28
0.1
0.4
1.16
2.67
0.25
0.05
0.09
1.34
1.14
24.35
13.33
42.65
4.62
13.80
25.08
15.35
11.65
5.82
6.73
Note. (X*-X**)/X*100= Gap quality percentage, X* is Calculated score and X** is
Predicted score and S.E. represents standard error percentage
Statistical Analysis
Four research questions were staged to address the problem that had not been
thoroughly reviewed in the past decade on RHMs literature. Each issue was assumed to
support previous studies’ proposition that the problem is more research is needed to
outline the neglected relationships of RHMs on rural communities. As presented in

Section 2, these four research questions serve as the basis for this study’s research,
design, and analytic, and are as follows:
RQ 1: Is there an association of healthcare transformation changes in structures,
processes, organizational culture, and values on clinical outcomes for rural
patients?
A Pearson regression model resulted in the null hypothesis being rejected. It
indicated that much of the increase in the likelihood of transformation changes
corresponded with the effect ratio of organizational complexities. This study suggests that
RHMs may be associated with impaired quality of care, clinical care turbulence, and
PSRs escalation. The model was statistically significant at p < 0.01, which means the
results suggested the alternative hypothesis (Ha1) failed to be rejected, and there was no
support for the null hypothesis (H01).
RQ2: What is the relationship between governance mechanisms and patient
outcomes in rural hospital mergers?
Hospital governance effect ratio displayed a weak association matrix result of (r =
-.733; p < .005). The model revealed hospital governance effect ratio had a weak
correlation between all 30-day mortality categorical and organizational synergies
complexity characteristics, and yet significant predictor to PSRs and CCDs in RHMs.
However, the model was statistically significant (p < .005), and the results demonstrated
that there was no enough support not to reject the alternative hypothesis (Ha2). RQ3:
How do best practices facilitate quality-focused initiatives and contribute to eliminating
unintended patient risks associated with structural changes and the process of care?

Hospital integration best practices was a relevant predictor of quality-focused
initiatives in eliminating unintended PSRs and CCDs in RHMs. Hospital integration best
practices effect ratio represented a correlation matrix results of (r = .367; p < .000). In
this model, results suggested the alternative hypothesis (Ha3) failed to be rejected, and
there was no support for the null hypothesis (H03).
RQ4: What is the relationship between clinician leadership and the quality of care
outcomes in RHMs?
Clinical leadership was a significant predictor of the quality of care in RHMs.
Clinical leadership ratio displayed a correlation matrix results of (r = .435; p < .002). At
p < .002, the study results revealed an alternative hypothesis (Ha4) failed to be rejected,
and there was no substantial support for the null hypothesis (H04).
The association between total hospitalizations, mortality rates, and currently
RHMs (nonprofit and for-profit hospitals) had a positive effect relationship and in both
surgical procedures and all medical conditions were statistically significant (p < .01) by
RHMs for the overall hospitalizations in this size category. In addition to substantial
variations in hospital performance profiles which were detected among 380 RHMs
(forprofit, and nonprofit hospitals) with a mean annual hospitalization on medical
conditions at 95% confidence level, had higher than expected mortality rates for all
metrics of 27.8% in total, which had a higher odds of poor hospital performance than
nonmerged hospitals.
Summary
Unsafe healthcare has always remained one of the challenges of the U.S.

healthcare delivery system and a well-recognized health issue, usually listed among the
top three causes of deaths in the United States with rural residents experiencing more
significant hardship (NC RHRPRC, 2014). Declines in hospital performance in the
quality of care have been associated with more frequent mortality and hospital
readmission rates. Several mergers are consummated to capitalize on new geographic or
demographic markets, expand product offerings, facilitate the acquisition of critical
employees, boost productivity, reduce competition by absorbing a rival company, or even
more long-term strategies (Botje et al., 2016). Amid the need to maintain such a
competitive advantage, healthcare administrators must perform the intricate task of
keeping pace with the robust healthcare environment – continually changing patient
volumes, increasing supply costs and quality requirements, personnel shortages, and
utilization standards. Regardless of the motive, the process and outcome must be
measured to assess, identify, and eliminate the root causes of poor performance during
and after the transition.
While the findings of the study revealed modest differences in the overall risk of
hospital readmissions and 30-day mortality rates among rural versus urban hospitals, it
did find that the location of the hospital and its acquired characteristics have a significant
effect on performance and patient safety levels. The study suggests that patients
discharged from hospitals in large RHMs had a 29.3% higher risk of unplanned
readmissions as compared to those released from for-profit and nonprofit urban hospitals.
Concurrently, the study found that patients treated at merged rural hospitals have an
average 8.5% higher risk of dying or experiencing one or more complications during a

hospital stay than if they were treated at nonmerged hospitals in that procedure or
condition. These findings further confirm the need for critical evaluation of commonly
known arguments that integrating health systems improves efficiency, access to care, and
quality of care, and may lower costs. Although integrating health systems may result in
financial and operational efficiencies, declines in health outcomes should be avoided. My
findings present an opportunity to identify systemic reasons for the higher PSRs and
CCDs observed in common medical conditions and after certain operations in RHMs.
The statistical analysis results revealed that all four null hypotheses could be rejected,
indicating that organizational synergies complexities represented by logistical differences
among RHMs all showed the trajectory persisted pattern of CCDs and PSRs. Section 4
will discuss and present a detailed synthesis of my study’s application to professional
practice, gaps in research, limitations and implications for social change. This section will
also list recommendations of the study and suggestions aimed at improving future
research in light of these study findings.
Section 4: Application to Professional Practice and Implications for Social Change
Introduction
As healthcare systems deal with the complex regulatory demands of the quality
improvement and quality control of healthcare, as well as the challenges of a shrinking
economy, there is always the possibility that one facility will merge with another.
Maintaining a hospital or health system is costly and combining health systems can help
counterbalance some of the financial burdens; however, those mergers may trigger more

than just performance dilemma. In the long term, hospital affiliations might cause an
upheaval of clinical disruptions and impact quality of patient care (see Hass et al., 2018)
Because RHMs often bring about changes in patient populations, activities adjustments,
and facility infrastructure, safety risks may increase.(see Jennings et al., 2008; Johar et
al., 2014). Researchers have identified these most pressing patient safety concerns that
may occur during mergers or system expansions to play a significant role in high
mortality rates and poor patient outcomes (Hass et al., 2018; Noles et al., 2015). The
burden affects nearly 60 million people who reside in rural counties across the United
States, resulting in over 440,000 deaths yearly, and many of these PAEs are avoidable
using system-oriented shared safety culture (CDC, 2017).
Adjustments of therapeutic activities proposed by leadership, down-sizing,
redistributions of staff, conflicting cultures, location changes, new settings for providers
and hospital structure fragments may all have unforeseen effects (Berg & Grimeland,
2013). Even though hospital mergers typically have several positive goals, arguments in
favor of a merger must be investigated carefully for idealistic oversight of the prevalence
of PSRs and CCDs of RHMs. In many cases, teams with narrow proficiency in patient
safety are typically responsible for implementing healthcare mergers, acquisitions, and
affiliations (AHRQ, 2018). Considering these issues, the primary objective of this study
was to examine the potential association of healthcare transformation changes in
structures, processes, organizational culture, and values on clinical outcomes for rural
patients post mergers. The focused intent of the study was to enhance the understanding

of the incidence of patient risks and clinical turbulence in RHMS as a basis to reduce
them.
In this quantitative analysis, I focused on hospital performances and quality
outcomes on RHMs and acquisitions that occurred between 2010 and 2018. Regression
analyses were conducted to examine the association between hospital performance safety
metrics that were categorized into the following six quality indicators: mortality, safety of
care, readmissions, patient experience, effectiveness of care, and timeliness of care. I
used hospital organizational characteristics, such as hospital size, urban/rural location,
ownership type, and teaching status as controls for factors that could influence this
association and provide some specifics on whether the impact of acquisitions might vary
over time. Publicly available data used in the study were from Medicare Mortality
Ratings Databases, the U.S. NVSS archives, Hospital Compare, Hospital Evaluation
Databases and hospital quality indicators from the CMS.
Interpretation of Findings
I proposed a theoretical lens for understanding and evaluating complexity in
integrating healthcare systems based on degrees of uncertainty and the involuntary nature
of many change processes and cultural clashes (see Resta, Sonnessa, & Tànfani, 2017).
Considerable concerns have been highlighted for why transformational changes, like
mergers and acquisitions, often lead to adverse health effects and increased CCDs.
Undoubtedly, systematic problems in clinical care turbulence are at the root of most
detrimental events that arise post mergers. Amid such complex mechanical and
organizational changes, the upheaval accompanying restructuring efforts through mergers

can also be related to lower job satisfaction among clinicians and increased burnout.
Furthermore, increased conflict fueled by differences between merging entities relating to
unique operation systems, mission, and values, often makes clinicians feel more uncertain
about their responsibilities, what is expected of them, and how the changes will affect
their patients.
The findings of this study highlight that RHMs have a significant effect on
increased mortality and declined health status in U.S. rural communities, showing a
catastrophic inequality burden emerging as a significant determinant of the health of
populations. The results indicate that mergers have a particularly significant effect on
PSRs during and after the consolidation taking place. Previous studies have reported that
healthcare mergers result in a more extensive health system offering financial incentives
to smaller hospitals, including upgrades to supplies and equipment; protocols, and
information technology, such as electronic patient records and security systems (Hass et
al., 2018). However, in the present study, I found that these changes in infrastructure
often create challenges for clinicians, and without planning, such changes can cause
significant patient risk. Because of the seriousness of long-term, disruptive work
environment and the high prevalence of clinical risks, RHMs have a substantial effect on
socioeconomic burdens, prolonged delays in treatment, and patients often experience
travel and distance barriers to get care. Managing the process of a merger better should
lead to a more cautious approach to the likely gains, provide an understanding of the
problems that are likely to arise in the period of change, and anticipate and avoid harmful
consequences.

Contrary to the findings of the Charles River Associates Report that mergers have
become one of the critical means through which hospitals can provide their communities
with high-quality, convenient, and cost-effective care by allowing hospitals to create
connected networks of care (see Noether, May, & Stearns, 2017). This study revealed the
primary impetus is often financial rather than clinical. RMHs can have substantial effects
on clinical care and patient safety, particularly when clinicians encounter changes in their
practice setting, patient population, or infrastructure. Routine tracking of potentially
excess mortality and admission rates from the various causes of risk in rural and urban
areas might assist public health officials in monitoring substantial rural health disparities
and selecting effective programs and policies to improve the health of residents of rural
areas. With the increasing trend of RHMs not slowing down, rural patients will require
these data to compare the service they receive from merging different hospitals. Such
findings should, therefore, be increasingly made more accessible to the public.
Limitations of the Study
I identified a few limitations concerning this quantitative study. The principal
limitation of this study is that data collected on Hospital Compare comes from hospitals
that discretionarily offer their data for public reporting, so it is possible that there was a
systematic scoring bias in hospitals’ performance reporting across all measures (see
AHRQ, 2016). Although this data set contains hospital-specific performance on the
process of care quality measures and patient experience of care measures for over 4,500
hospitals, such a data set is vulnerable to the incompleteness of reporting. Its vulnerability
lies in the fact that hospitals can designate to submit data for all the quality indicators or

can elect to withhold the data from display on Hospital Compare if specific core measure
scores were particularly weak. However, CMS star rating reports have been used broadly
for hospital quality benchmarking, including analyses of the diagnoses used in my study,
and such benchmarking is valid compared with clinical data and large administrative data
sets. To include as many hospitals in my analyses and to reduce the variability in these
measures of quality, I combined the six separate outcome measures tracked by CMS into
three composite outcome indices: one for mortality, one for readmission, and one that
combined both mortality and readmission measures.
Secondly, the precision with which hospital performance can be ranked is
impacted by variations in hospital capacity, the class of subjects they care for, and
sampling strategies, (i.e., the numbers of patients used to calculate reported performance
rates from the quality measures). The only process of care measures applied to compute
rankings consists of one comprehensive prevention measure and mechanism of care
measures from six clinical topic areas: mortality, safety of care, readmissions,
patientcentered score, effectiveness of care, and timeliness of care. Even within these
specific clinical areas, they reflect only a portion of the hospital performance score
rankings.
However, despite limitations (i.e., lack of clinical detail, susceptibility to patient bias and
health literacy levels., time lags, and variations reporting systems), quality improvement
experts view public data as a possible and valuable source to evaluate hospital quality
performance.

To neutralize the severity of these data constraints, I used other data sources that
can provide information about healthcare quality in this study. Publicly available
Medicare Mortality Ratings Databases, Walden University Library databases, and
Hospital Evaluation Databases were used to assess whether the toll of specific mortality
diseases is worsening or decreasing, and to understand where best to target medical
interventions so they can play a critical role. Recognizing these limitations, I believe the
merits of the public data set outweigh many of these concerns and that it enabled a robust,
timely analysis of clinical outcomes with a validated data source and was highly relevant
to assessing the effects of the RHMs (see Loehrer, Chang, & Scott, 2018). Specifically,
ratings, such as Hospital Compare and CMS quality reporting measures, as well as other
sources included in the study, such as AHA reports, strengthen accountability and offer
differing arrays of performance measures that may induce hospitals to improve their
quality of care.
Gaps in Research
The findings of this quantitative study have shown the need for better planning,
and critical consideration in many areas of measure of success that can identify and verify
practices that improve safety in RHMS and that before strategic hospital merging
arrangements can be pursued, significant gaps in knowledge must be filled. Clear
recognition is needed in all three of the domains of patient safety areas identified: poor
outcomes of care due to PAEs, structural enablers to unsafe care, and disruptive processes
of care that lead to safety risks. In this era of closer scrutiny of cost and quality of care,

the field of hospital consolidation lacks actionable and outcome-oriented measures in this
area.
In this respect, understanding the true needs of the affected rural patients
generates an impetus for much fundamental work with integrating health systems and
their representatives in order to transform the present situation. However, lack of
methodological uniformity in the identification and measurement of PAEs, including
mismatch cultures and weak evidence-based best practices related to quality
management, continues to delay the development of knowledge about which
interventions should be adopted and how to encourage adoption of patient safety
practices.
Recent studies have examined the effects of changes in the health care market
segment on healthcare organization performance due to hospital merger expansions.
These studies have confirmed that the pursuit of economies of scale and coordinated care
initiatives have led to the escalation of price competition among hospitals and that price
competition has resulted in lower rates of cost growth, lower prices and price-cost
margins, and changes in the adoption and use of technology (Haas et al., 2018; Loehrer,
Chang, & Scott, 2018; Noles et al., 2015). However, the effects of changes in health
structure on the quality of care provided by hospitals after a merger are less well
understood, and this complex changing environment lacks functional and
outcomeoriented measures in this area. In this study, I offer tactical recommendations for
future measure performance and endorsement to close this vital gap. The study
recommendations can be instrumental in organizing measure development efforts to

ensure that clinical, financial, and human resources are strategically targeted during the
transition and post merger phase.
Recommendations
As found in this study, the U.S. hospitals have been merging at a rapid pace for
more than 2 decades, forming influential organizations that have been creating countless
long-term, challenges for clinicians and significant PSRs. The current understanding of
the extent of CCDs and PSRs in RHMs and in their causes are underestimated. This is
especially true for rural hospitals and those with integrating systems in transition, where
most of the U.S. rural population lives and receives health care from. There are even
substantial gaps in our knowledge about how to minimize the PSRs and address clinical
turbulence in RHMs, often brought about by changes in patient populations, activities
adjustments, staff distributions, and facility infrastructure.
Although some strategies have been developed, the U.S. health services know
little about how to address many of the problems identified. Adopting and implementing
patient-centered strategies to improve the patient safety culture model will be the first
step. Presently, potential or actual adverse events (e.g., mortality rates and hospital
readmissions) are substantially underreported, and healthcare organizations will require
the identification of specific areas where system complexities slow or inhibit progress and
the development of solutions geared toward overcoming impediments and failures (IOM,
2011). Achieving this objective will require that healthcare administrators and
developmental business leaders become aware of patient-centric and embrace valuebased
healthcare practices when entering consolidations.

Aiming at the efficiency build up and focusing on strengthening capacity for
patient safety initiatives, various steps must be taken to foster a complete successful
patient safety culture model in RHMs. A few of the most critical areas to consider when
constructing an operational efficiency for merging health systems include a clear
leadership structure, system-oriented shared safety culture, commitment to the
standardization of clinical best practices, and well-defined ground-level integration
strategy. Given the many variables and catalysts influencing the systematic change in
U.S. rural hospital delivery services, careful planning, thorough due diligence, and
strategic integration post transaction can simplify the process to overcome poor patient
outcomes stem from systemic failures in the delivery of care.
Previous research suggests that organizational culture affects the success of
postmerger integration and clinical collaboration (Ovseiko, Melham, Fowler, & Buchan,
2015). A further increasing body of literature advocates that rural hospitals often lack the
necessary means to adopt patient safety strategies commonly found in more extensive
facilities due to organizational, technological, staffing, and financial constraints (Coburn,
& Gage-Croll, 2011). This research, however, aims to provide a framework for attaining
the full benefits of a merger — operational efficiencies, economies of scale,
organizational performance and enhanced clinical value.
Research advocates that many mergers or consolidations do not go according to
plan or fail to achieve the expected outcomes, and culture is often the driver of such
failure. Although there are innumerable factors that can lead to merger and acquisition
failure, cultural mismatch is one of the mentioned reasons. To overcome the risk of

failure, the integrating health systems must focus on understanding and developing the
new entity safety culture. While overcoming barriers of learning may take several years,
experts in merger and acquisition deals suggest that leaders from the acquiring facility
should consistently and frequently articulate the mission and goals of the transaction.
From the expansive view of mission statements to the fine details of daily schedules,
communications should focus on supporting integration efforts and building the
foundation for a typical patient safety culture between the organizations. By incorporating
this approach, developmental leaders could help ensure that RHMs go according to plan
and achieve their desired results.
Further research is recommended to help healthcare organizations understand and
quantify patient safety events and areas of vulnerability in their institutions post mergers.
It is feasible that gaining a better understanding of the systemic factors that combine in
unanticipated ways and threaten patient safety may also help to shape a successful
hospital alliance. While the study outlined a measure of success in identifying and
verifying practices that improve safety, more work is required in authenticating how best
practices get executed and amalgamated into clinical processes, and in corroborating,
there is a full and continual commitment to providing the safest care possible. Finally, I
recommend this study be expanded to hospital mergers in U.S. metropolitan areas to
ensure this commitment does exist throughout the continuum of care. In addition to
evaluating hospital performance differences post mergers, future investigators will have
the potential to provide more insight regarding the motive behind mergers and acquisition
transactions among rural hospitals.

Implications for Professional Practice and Social Change
Professional Practice
As health systems struggle amidst regulatory changes, short cut in Medicare and
Medicaid payments and shrinking profits, a merger can seem like precisely the cure-all
needed to ensure survivability. Owing to this preposition, rural hospitals are attractive
targets, and the trend of RHMs is likely to continue. Given the critical need for health
services and obstacles to access to care of rural citizens in the United States faces, it is
particularly important to understand any impact to the community caused by these
monumental transactions. Despite the benefits of the mergers and acquisitions, patient
care and safety must be prioritized both during and after the transition. Studies of this
kind are essential to set a foundation of a proactive, purposeful and sustained patient
safety model which includes integrating cultures into the organization and deploying
best-practice merger and acquisition project management techniques and aligning
executive and functional leadership.
Policymakers and developmental business executives must understand that
integrating two or more organizations into one cohesive operating unit takes intense
planning and a focus on post merger logistics. Inherent in that melding necessary steps
are cultural assimilation, process communication, technology, and system integration.
Understanding these tasks and being aware of potential correlations that exist potential in
healthcare transformation changes in structures, processes, organizational culture, and
values on PSRs and CCDs for rural patients after mergers, could facilitate healthcare
executives to identify high-level strategies on quality improvement. By studying quality

indicators carefully in RHMs and raising institution awareness of efforts to reduce
inpatient mortality and PAEs in underserved communities, I hope to have provided a
holistic view into long-term implications and other operational community factors.
Positive Social Change
With hospital mergers on the rise, organizations that invest in building active
patient safety cultures stand to benefit. Understanding and properly implementing quality
improvement initiative is essential to a well-functioning health system and is necessary
for any practice interested in improving performance, patient safety, or clinical outcomes.
In addition to identifying opportunities for quality improvement, foster a commitment to
excellence, a measure that carries significant emotional weight, as well as essential
implications about quality of care, is a hospital's mortality rate. Through this study
results, I hope to support this commitment by helping health care leaders understand how
reducing hospital mortality rates and eliminating PAEs can improve health care safety
and the quality of care delivered to rural patients. While PSRs and CCDs in the U.S. rural
hospital delivery services may vary widely when calculated systematically and
categorized according to the level and type of care, patterns emerge that can highlight
system defects. Although several studies have documented the need for U.S. Hospitals to
reduce inpatient mortality rates and PAEs, there is a scarcity of literature on effective
methods to accomplish this goal. Therefore, this research study adds to the knowledge
needed for policymakers to make decisions and establish a nationwide systematic process
and develop a stronger culture of continuous quality improvement in RHMs.

Conclusion
Several recent articles cited RHMs may affect the delivery of quality of care and
shrink the availability of services as hospitals work toward greater efficiency in cost
control (National Rural Health Association, 2015). When financial performance becomes
the goal, fragmentation of productive tasks, down-sizing, redistributions of staff,
conflicting cultures, location changes, new settings for providers, and hospital structure
fragments may all have unforeseen effects. All these factors affect a community and play
a significant role in the prevalence of mortality, hospital readmission rates, and complex
clinical disruptions. Whether the primary driver of a merger is the pursuit of economies
of scale, the ability to decrease unit costs or improve productivity and outcomes through
increased volumes, there is a problem with the quality, efficiency, and patient safety in
the U.S. rural healthcare delivery, mainly related to RHMs (CDC, 2017; NC RHRPRC,
2014; Unger et al., 2018).
The examination of processes provides the critical information that can be acted
upon, establish strong relations between structures and outcomes, and promote strategic
collaborations among integrating systems. Minimizing PAEs requires a greater
understanding of the causes of these events, especially in merging entities. As such, this
study provides a framework for policymakers to identify critical aspects of patient safety
and eliminate the structural features of health systems and the processes of care that lead
to adverse events. Given the recent emphasis on planning patient safety improvement
interventions targeting rural hospitals, I recommend more research is needed on patient
safety in those circumstances. In particular, the study findings justify the urgent

development of interventions designed to reduce the episode of unsafe healthcare
experienced by rural patients after mergers.

