


INTRODUCTION American hospitals and health systems
“Healthcare in the U.S. is in a state of hyper-turbulence characterized by accumulated
waves of change in payment systems, delivery systems, technology, professional relations,
and societal expectations” – Shortell, Gillies, & Devers, 1995.
American hospitals and health systems merge for a wide variety of reasons but
always with one common, overarching goal: achieve some significant, tangible gain for
the organizations involved (Brooks & Jones, 1997; Haspeslagh & Jemison, 1991). Some
stand-alone hospitals seek the protection and additional resources that a larger system
may bring (Dunn, 2013; Vogel & Hadfield, 2017). A rural hospital may opt to merge to
avoid closure or bankruptcy, thereby ensuring access to care for the remote, vulnerable
population it serves (Noles, Reiter, Boortz-Marx, & Pink, 2015). Two not-for-profit
health systems may merge as a way to preserve and enhance their ability to fulfill their
religious, charitable, or philanthropic mission (Cutler, 2000). Two for-profit, publicly
traded hospital companies may decide to consolidate in an effort to streamline operations,
decrease costs, increase profits, and maximize shareholder value (Cutler, 2000).
Regardless of motivation, senior management and the boards of directors involved with
the decision propose that a merger is the best overall strategic option for the future of the
organizations; combining the assets and resources of the organizations enhances their
ability to meet the health care needs of the patients and communities they serve. It takes
many years to determine whether or not a merger achieved its intended goals and fulfilled
the original promise. In most cases, the legal, financial, accounting, and regulatory work
required to complete the merger transaction is much easier than executing the post-
merger plan and making the merger work (Appelbaum & Gandell, 2002). The benefits of
a merger can accrue to the enterprise, shareholders (for-profit health system), bondholders
(not-for-profit health system), senior management, employees, physicians,

purchasers/payors, communities, and patients. However, a merger usually results in
winners and losers; the advantages of a merger may be enjoyed by a few stakeholders
while disadvantaging others (Blair, Durrance & Sokol, 2016).
The term “Total Net Welfare” (TNW) was developed by Katona and Canoy
(2013) to compute and express the net effect of a hospital or health system merger on a
given regional market. TNW is broadly defined as the sum of the positive and negative
welfare impacts of the merger. For example, a hospital merger may result in improved
quality performance (a positive impact) and higher prices (a negative impact). Katona and
Canoy found that hospital mergers directly and indirectly affect patients, employees
working for the merging organizations, local and regional employers who provide health
insurance for their employees, health insurance companies and health plans, physicians,
and many others. Every hospital merger has advantages and disadvantages.
To the extent the positive impacts outweigh the negative impacts, the merger has a
positive TNW. Conversely, if the merger-related disadvantages exceed the advantages, the
merger has a negative TNW. The TNW model attempts to incorporate all elements
affected by the merger including quality, safety, access, efficiency (costs), pricing, and
service. Positive impacts of a merger may include improvements in quality or safety
performance, better access to care, lower costs for care, increased investments in public
health initiatives, better online access to health information, lower pricing for health
insurance premiums, new services offered, incremental investments in technology, and
better service for patients (i.e., improvements in the patient experience). Negative impacts
involve the opposite: lower quality or safety performance, diminished access, higher
costs, and decreased service.
The vast majority of mergers across all industries and time periods either fail or
do not achieve their goals (Bergh, 1997; Gugler & Yurtoglu, 2008; Montgomery &

Wilson, 1986; Ravenscraft & Scherer, 1997, 1989; Tichy, 2001). Research conducted by
economists, business consultants, sociologists, psychologists, and organizational behavior
experts have identified numerous factors associated with merger failures or poor
postmerger performance. In the vast majority of cases the primary culprit was the
inability of the two organizations to address critical human factors by successfully
combining, blending, and harmonizing culture (Chakravorty, 2013; Ettore, 1999;
Grossman, 1999; Segil, 1998; Tompkins, 1998).
Research conducted by Hellriegel, Slocum, and Woodman (1976/1986) found
even two companies operating in the same industry/market, serving the same region, and
sharing common customers, may evolve and establish two very different and distinct
cultures. Cultural problems and conflict among senior management disrupt, handicap, and
hamper the newly merged organization. The underlying strategic, operational, and
financial rationale is usually sound and fully justifies the merger decision. However, the
lingering human factors and social phenomena that accompany a merger are oftentimes
underestimated or overlooked (Chakravorty, 2013).
Merger and Consolidation Trend
The U.S. health care industry is experiencing a time of uncertainty, volatility,
unprecedented change, and transformation (American Hospital Association, 2016;
American Public Health Association, 2016; Britnell, 2015; Pearl, 2015). The U.S.
Congress and President Trump intend to significantly revise or completely replace the
Affordable Care Act (ACA), which creates more uncertainty and, potentially, more
upheaval within the health care industry. New value-based reimbursement models,
implemented under the ACA, have reformed the way hospitals and physicians coordinate
and deliver care (Deloitte, 2015; Fried & Sherer, 2016). Regional integration efforts are
accelerating as hospitals, physicians, self-insured employers, health insurance companies,
suppliers, and other stakeholders align and connect their activities around a new
paradigm: population health (Franz, Skinner, & Murphy, 2016).
In the 25-year period between 1990 and 2015 there were 2,748 consolidation
transactions (horizontal mergers, acquisitions, and other formal integration/alignment
arrangements) involving U.S. hospitals and health systems (Maslan & Johnston, 2016).
During the 1990s, approximately 900 hospital consolidation transactions occurred,
leading to the formation of many regional health systems (Patrick, 2014). Following this
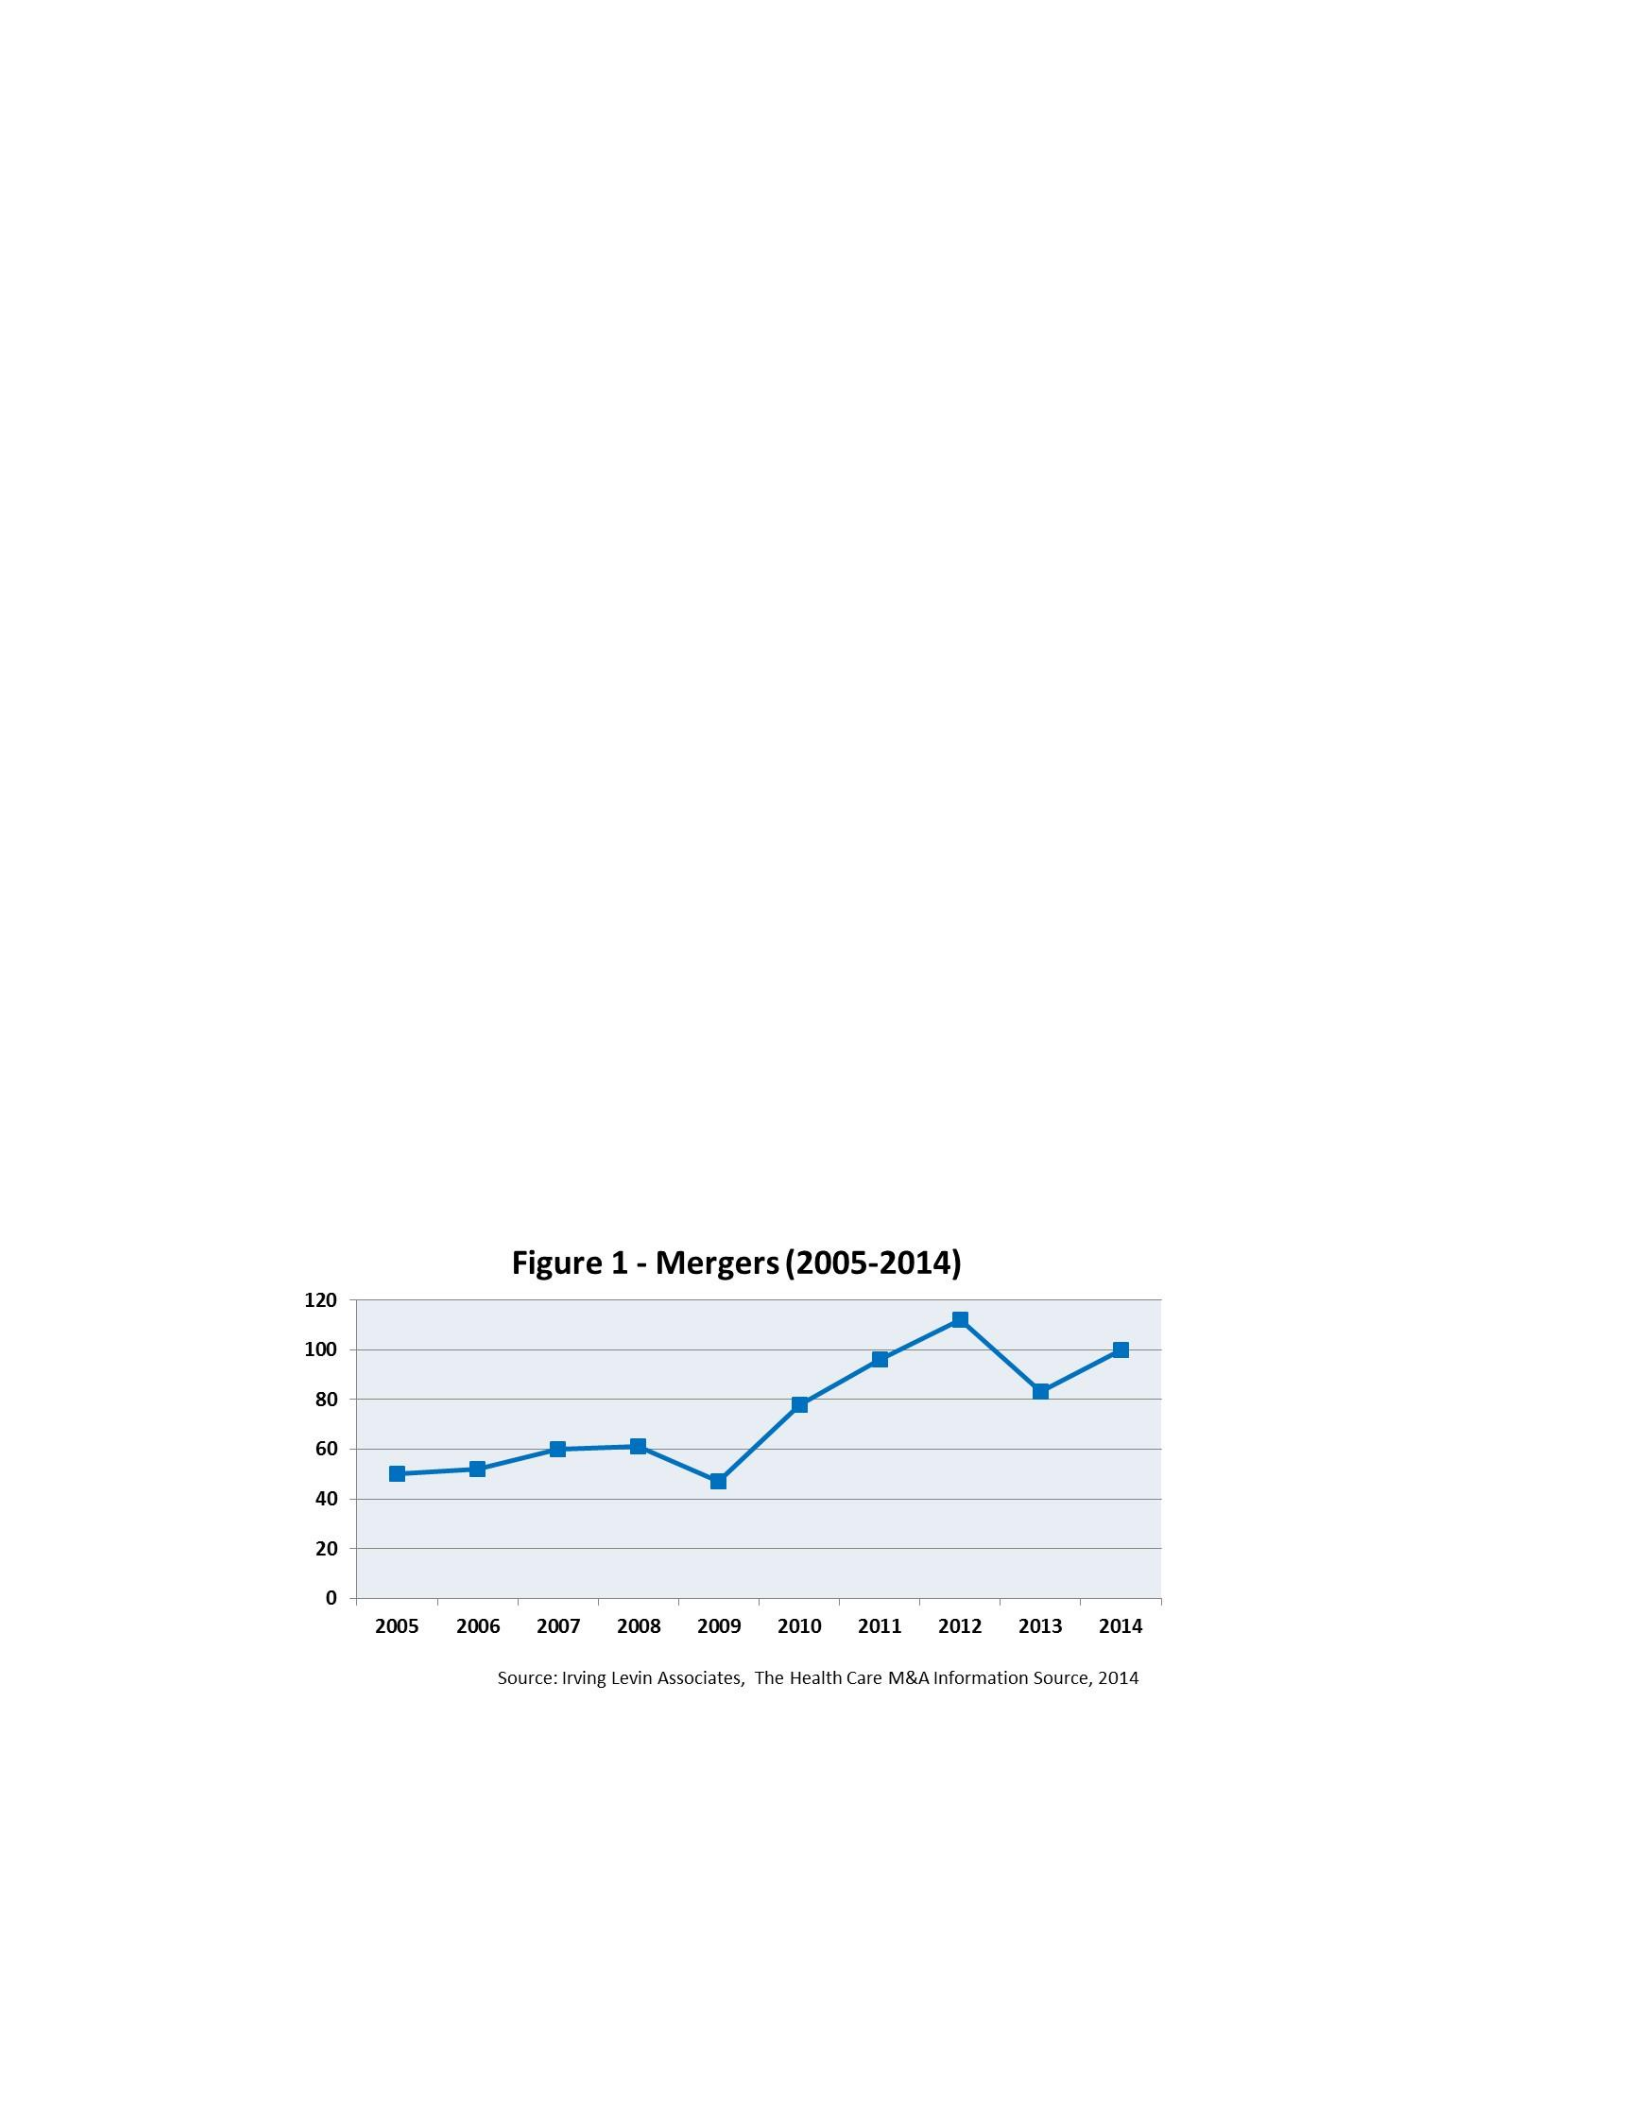
surge in the 1990s, the pace of consolidation slowed. However, since 2008 the number of
consolidations has increased substantially (American Hospital Association, 2013, 2015;
Levin Associates, 2015; PWC, 2015; Summer, 2010; Vaida & Wess, 2015; Wirtz, 2015)
(see Figures 1-3). Many industry experts call for this trend to continue for the foreseeable
future (Guerin-Calvert & Maki, 2014; O’Connell, 2015; PWC, 2015; Vaida & Wess,
2015). Eighty-two percent (82%) of hospital CEOs surveyed at the end of 2015 stated
that their organization was either “likely” or “very likely” to undergo a consolidation
transaction within the next five years (Illinois State Medical Society, 2016).
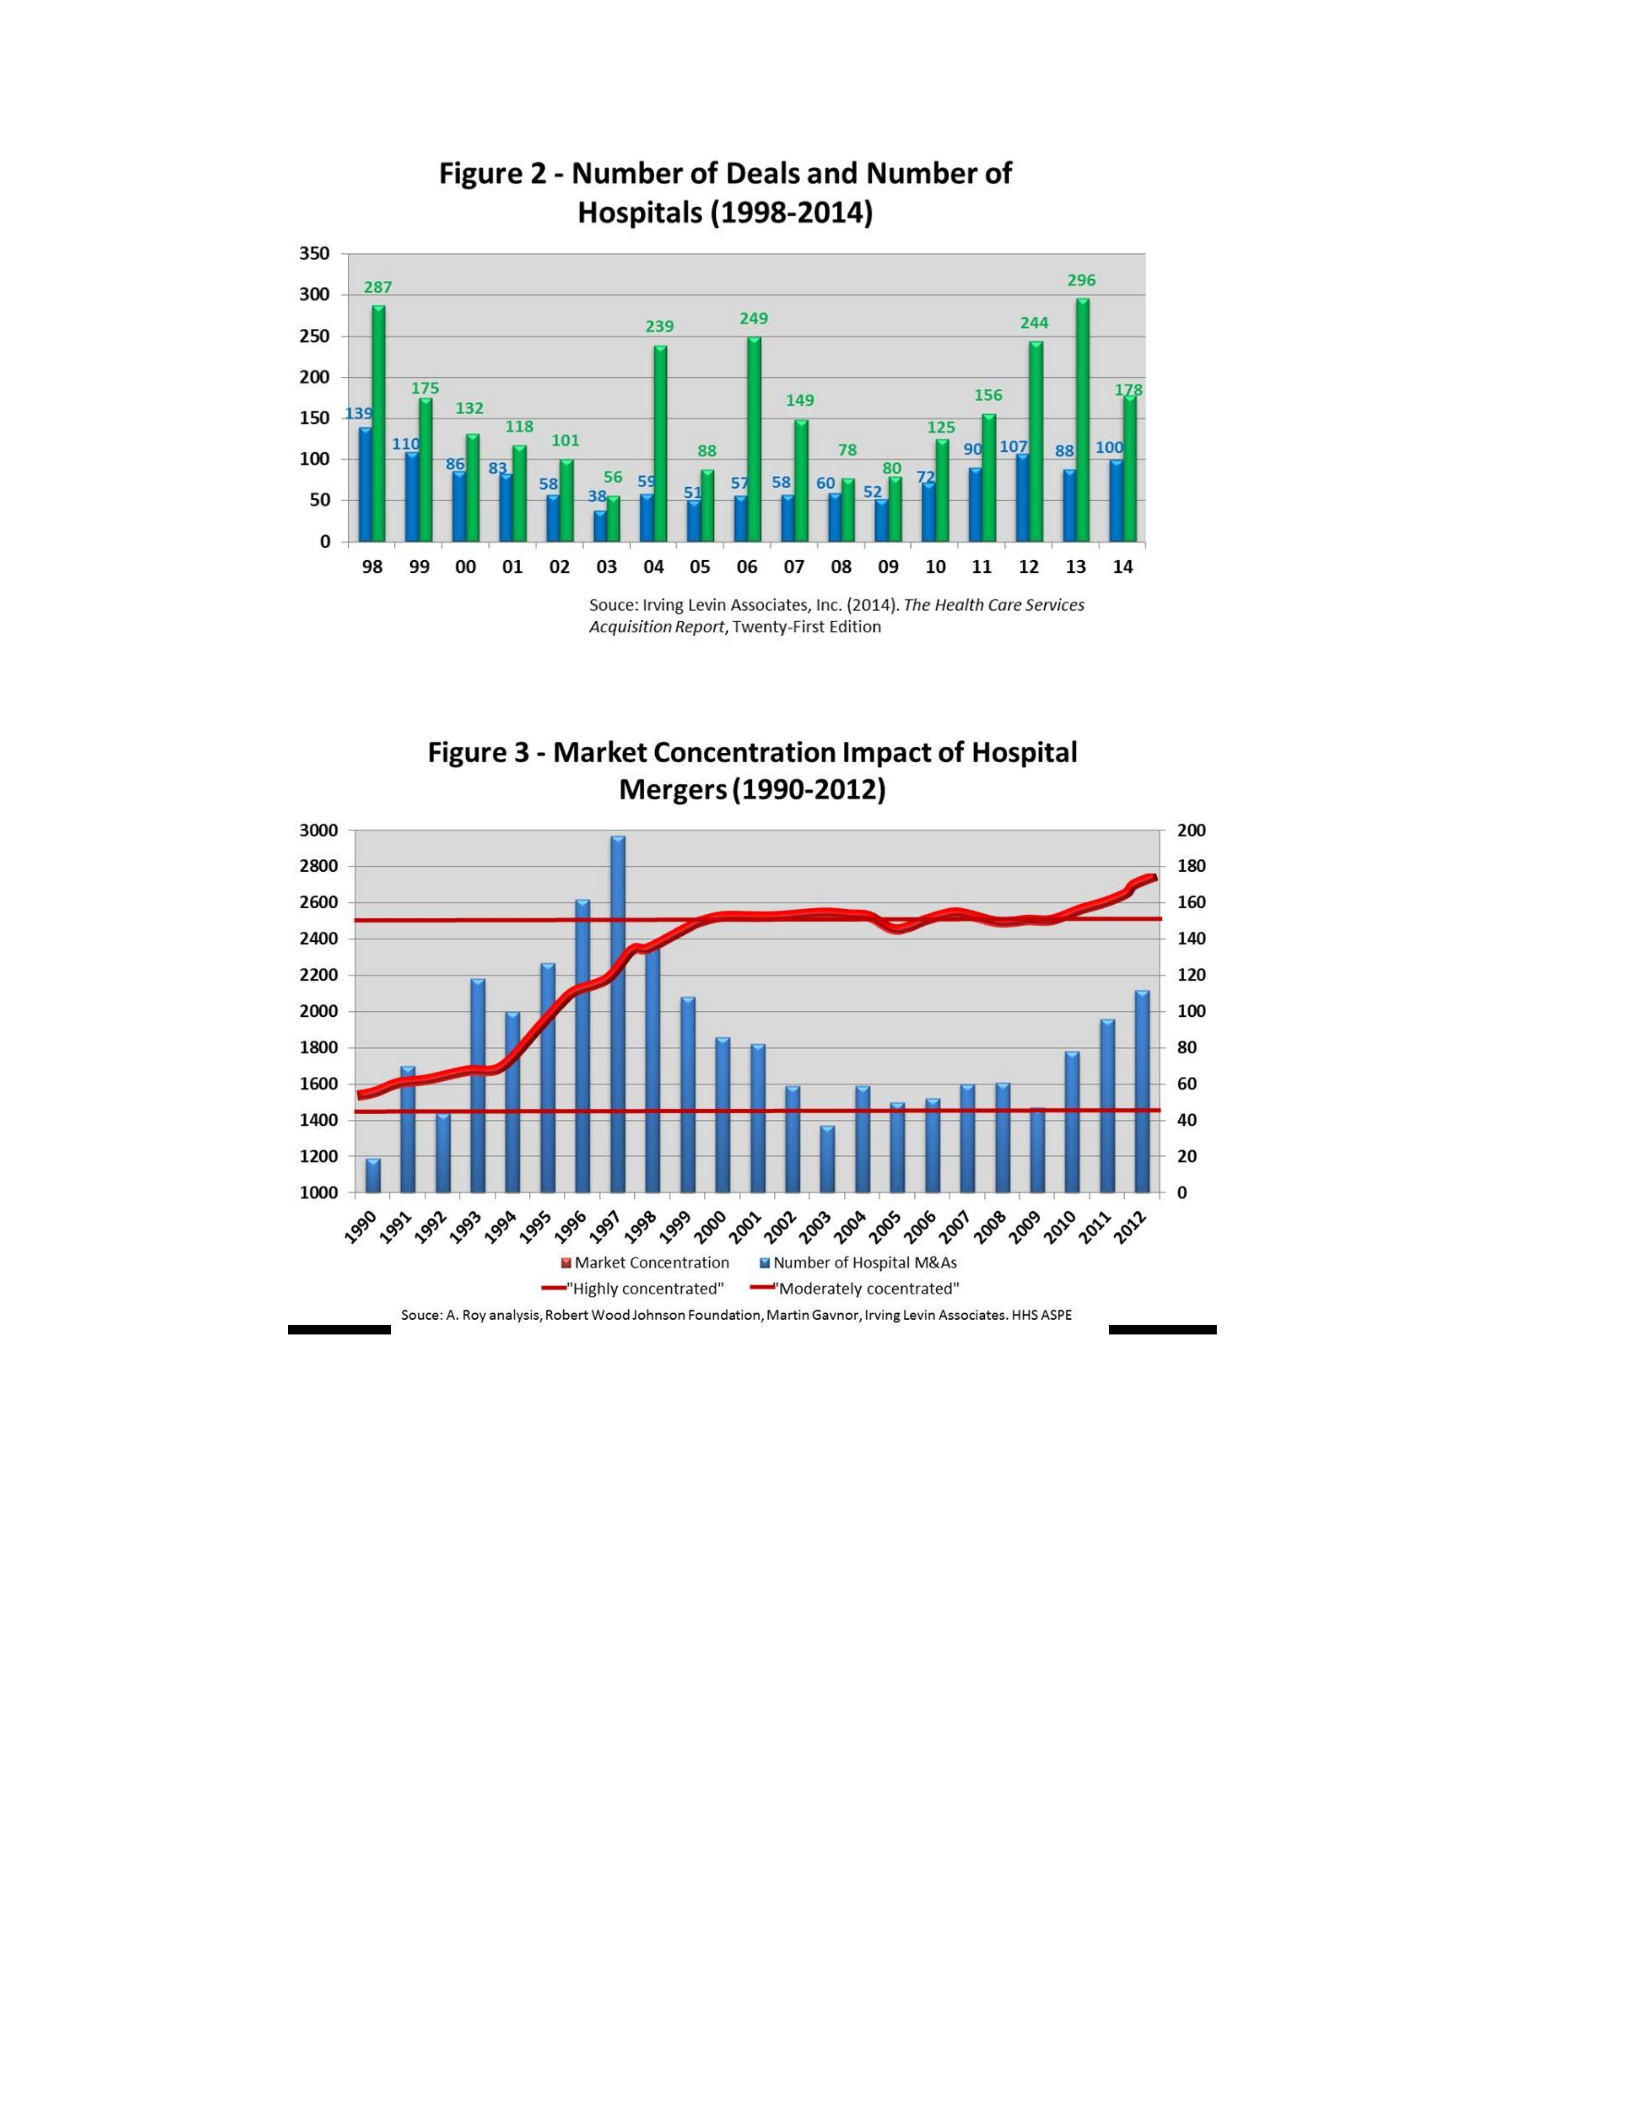
Blue bar = number of deals; green bar = number of hospitals
Some health care futurists predict continued consolidation will lead to
“megasystems” that will compete with other mega-systems over large, multi-state regions
(Deloitte, 2014; Ellison, 2016; Evans, 2014; Herman, 2014). Deloitte (2014) forecasts a
50% decrease in the number of health systems over the next 10 years. Morrison, health
care futurist, stated “[w]e are moving pretty rapidly toward a situation where 100 to 200
large, integrated regional health systems” will dominate American health care (GE
Healthcare, 2014, p. 3).
Do Hospital Mergers Create Value?

In light of the merger wave and large-scale consolidation of health care providers,
many researchers, government regulators, elected officials, and consumer groups have
asked these key questions: Do hospital and health system mergers create value? In other
words, do mergers result in an increase in TNW (Total Net Welfare)? How do mergers
affect quality, safety, access, cost, pricing, profitability, and service?
As will be discussed in Chapter 2, hospital mergers have been thoroughly
examined over the past 25 years. Many studies have analyzed the merger impact on
clinical quality and safety performance. Several researchers evaluated the merger effect
on access to care especially for at-risk, vulnerable, under-served, remote, or rural
populations. Numerous economic studies examined the impact of mergers on internal
operating expenses; pricing (i.e., fees charged to insurance companies, health plans and
patients); health insurance premiums; operating margins; and profits. However, there is
no published study that assesses the impact of hospital mergers on customer service in
terms of patient experience or how patients perceive and rate their inpatient care episode.
Statement of the Problem
Due to mergers and acquisitions, American health systems are growing larger in
terms of number of hospitals, hospital beds, and annual revenues. As consolidation
occurs, hospital market concentration has increased substantially. Applying the
Herfindahl-Hirschfield Index (HHI), the majority of metropolitan areas in the United
States are considered “highly concentrated” (National Academy of Social Insurance,
2015). The more highly concentrated a market becomes, the less competitive it becomes
(Archer, 2013).
In light of the growing consolidation and concentration of hospital services across
the United States, several questions arise:
• What incremental value is generated from consolidation?

• How do hospital mergers affect hospital performance from a quality, safety,
access, efficiency, pricing, and service perspective?
• How do hospital mergers affect patients and the communities served?
• What benefit do patients and communities receive?
Significant research has been conducted in the past 25 years to address these
questions. Most of the research treated the merger as the independent variable and
examined the impact of the merger on various performance-related outcomes: quality,
safety, access, internal operating costs, pricing, operating margin, and insurance premium
pricing. Some studies applied a difference-in-differences statistical method while others
compared an intervention group of merged hospitals with a control group of hospitals that
did not merge. While several authors found a positive correlation between mergers and
certain performance outcomes, the vast majority of studies found no effect or a negative
effect (Gaynor & Town, 2012; Universal Health Care Foundation of Connecticut, 2014).
One significant gap exists in this comprehensive body of merger-related research: no
study has examined the relationship between hospital mergers and patient experience.
Patient Experience Background
American hospitals began using formal surveys in the early 1990s to obtain
feedback from patients to improve service and, thereby, increase patient loyalty and
preference (Fottler, Ford, & Heaton, 2002). Starting in 2007, in an attempt to objectively
measure patients’ perspectives on hospital care, the Centers for Medicare and Medicaid
Services (CMS) began requiring all acute care hospitals to report patient experience
scores as a condition of receiving Medicare and Medicaid payments. CMS stipulated the
use of a survey instrument jointly developed by CMS and the Agency for Healthcare
Quality and Research: the Hospital Consumer Assessment of Healthcare Providers and
Systems Survey (HCAHPS). Standardized and publicly reported, HCAHPS provides a

tool for comparing a patient’s perception of care delivery/service (i.e., patient experience)
within and between hospitals. Beginning in 2013, HCAHPS performance became part of
CMS’s Value-Based Purchasing program. Not only is reporting HCAHPS scores a
requirement for receiving any CMS payment, a hospital is subject to additional financial
penalties based upon its HCAHPS performance (CMS, 2017).
Significance of Study
This study provides a unique perspective which adds to the extant research on
hospital mergers. A hospital’s service performance, as measured by HCAHPS ratings and
scores, is a core component of value definition. Patient experience is part of the TNW
equation; it addresses whether or not a merger positively or negatively affects the service
patients (consumers) receive from a hospital.
Mergers are oftentimes controversial events. The increasing size and market
concentration of hospitals and health systems is of particular interest to state and federal
government regulators, the Federal Trade Commission, the U.S. Department of Justice,
consumer watchdog groups, elected officials, physicians and physician group practice
associations, nurses and nursing organizations, policymakers, and health care
administrators. Determining how mergers impact patient experience is an important
contribution to the overall evaluation of the consolidation of health care services.
Statement of Purpose and Research Questions
The purpose of this study was to examine the overall relationship between
hospital mergers and patient experience (measured with HCAHPS) and answer the
following five research questions:
1. Prior to merger, do hospitals pursuing a merger have different HCAHPS scores
compared to similar hospitals that are not pursuing a merger?
2. How does a merger affect HCAHPS performance?

3. Does time play a role in this effect? In other words, as more time passes
postmerger, does any difference in HCAHPS performance disappear?
4. Does the type of transaction (merger-of-equals vs. acquisition) moderate this
relationship?
Summary
In the past 25 years, the vast majority of U.S. hospitals have, through merger or
acquisition, become part of large health systems serving multiple geographic markets
and/or regions of the country. Since 2008, another wave and magnitude of consolidation
has occurred with many multi-hospital systems merging with other multi-hospital
systems forming mega-systems. This significant and unprecedented level of
concentration raises many regulatory and economic concerns about the net value (i.e.,
sum of positives and negatives) of mergers on patients, payors, employers, and the
communities impacted. Understanding the association of hospital mergers with patient
experience is an important component of that impact/value analysis. The aim of this study
was to provide unique insights and help policymakers and health system leaders evaluate
hospital consolidation decisions.
CHAPTER 2
LITERATURE REVIEW, CONCEPTUAL / THEORETICAL FRAMEWORK,
AND STATEMENT OF HYPOTHESES
“The emotions surrounding a merger are much like getting married and divorced in the
same day” – Bruhn, 2001.
This chapter opens with a literature review followed by a presentation of the
conceptual framework and pertinent theories that support and underlie the hypotheses.

The chapter ends with a statement of 12 hypotheses that were empirically tested through
this research study.
The literature review section is comprised of the following four sub-sections:
A) review of empirical research involving the evaluation of patient experience
in the hospital setting;
B) review of research involving the impact of mergers on customer satisfaction;
C) review of research on post-merger hospital performance; and
D) review of research on the post-merger disruption effect.
Literature Review
Sub-Section A – Literature Review on Patient Experience and Satisfaction
Managing Patient Experience Is Critical to Hospitals
Patient perceptions of their inpatient experiences and their overall satisfaction
levels (as measured by the Hospital Consumer Assessment of Healthcare Providers and
Systems, [HCAHPS]) are important strategic considerations for most hospitals. Hospitals
with comparatively high patient experience ratings enjoy a better image and reputation
(Andaleeb, 1988). Consequently, they also may have a distinct competitive advantage in
their market area (Hall, 2008). In addition, several authors have found a positive
relationship between a hospital’s patient experience performance and financial
performance (Charmel & Frampton, 2008; Deloitte, 2016; Hall, 2008; Richter &
Muhlestein, 2017).
One patient’s bad experience, and the resulting negative word-of-mouth, can cost
a hospital between $6,000 and $400,000 in lost lifetime revenues (Strasser, Schweikhart,
Welch, & Burge, 1995). Hospitals must be as aggressive as other service industries at
creating loyalty and customers for life (Carrus, Cordina, Gretz, & Neher, 2015; Spoerl,
2012; Zeithaml & Bitner, 2000). Research conducted by Reichheld and Markey (2011)

found that a hospital’s overall HCAHPS performance had a positive relationship with
repeat and referral business. The increasing role of patients in the selection of their
hospital (i.e., patient preference versus physician choice), coupled with public reporting
of HCAHPS scores, are driving more hospitals to make patient experience a top strategic
priority (Reichheld & Markey, 2011).
Due to the nature of how the CMS value-based purchasing program’s penalty for
HCAHPS is computed, hospitals must continuously improve HCAHPS scores in order to
maintain their relative performance. Avoiding the HCAHPS-based financial penalty
requires increasing expertise, effort, resources, and financial investments (Stanowski,
Simpson, & White, 2015).
Determinants of Patient Experience
Empirical research conducted over the past 20 or more years has identified
numerous factors that influence and determine patient perceptions of their inpatient
experience. Clinical quality (competency of staff and clinical outcomes) and safety
(absence of harm) are two factors but difficult for patients to accurately measure due to
their “inherent intangibility, heterogeneity and inseparability features” (Conway &
Willcocks, 1997, p. 132). Convenient access and availability, assessed by geographic
location and waiting times, are important elements and easily evaluable (Tucker, 2002).
The appearance and condition of the physical facility (exterior and interior), sound levels,
food quality, and overall cleanliness influence patient perceptions, experience, and
satisfaction (Swan, Richardson, & Hutton, 2003; Woodside, Frey & Daly, 1989).
However, the most influential factors affecting the inpatient experience involve
human interaction and service delivery. These factors include communication (explaining
things well and listening), responsiveness, timeliness, courtesy, respect, empathy, concern

about pain management, compassion, friendliness, staff demeanor, and the amount of
interaction time with nurses and physicians (Boshoff & Gray, 2004; Fowdar,
2005; Tucker & Adams, 2001; Ware, Davies-Avery, & Stewart, 1978).
Link between Employee Satisfaction and Patient Experience Performance Many
companies, representing the full gamut of service industries, have found a link between
employee satisfaction and customer satisfaction (Brown, 2005). An extensive meta-
analysis of empirical research on customer service performance in the banking industry
found a strong correlation between employee satisfaction and customer loyalty. This
same analysis found evidence to support causation: happy employees provide better
service leading to higher customer satisfaction (Anastasiou &
Nathanailides, 2015). Research in the hospital setting resulted in similar findings. Larson
(2004) combined the surveys of 50,000 hospital employees from 33 hospitals with 20,000
patient experience surveys. The conclusion was that higher levels of employee satisfaction
were strongly associated with higher levels of patient experience performance.
Research with Patient Experience (HCAHPS) as the Dependent Variable
Mazurenko, Collum, Ferdinand, and Menachemi (2017) conducted a meta-
analysis and systematic literature review focusing on predictors of hospital patient
experience as measured by HCAHPS. Twenty-nine of the 41 studies evaluated involved
hospital-level predictors. Certain organizational and working environment attributes were
positively associated with HCAHPS performance including well-defined nursing
standards (Kutney-Lee et al., 2009), cultural competency (Weech-Maldonado et al.,
2012), and staff perception of a safety culture (Sorra, Khanna, Dyer, Mardon, &
Famolaro, 2014).
Kutney-Lee and colleagues (2009) conducted the first study to explore how nurse
working environment and patient-to-nurse ratios affected HCAHPS scores. Working

environment was measured using a widely recognized and standardized tool, the Practice
Environment Scale of the Nursing Working Index. More than 98,000 hospital-based
nurses responded to the survey. The authors found that the nurse working environment
had significant effects on HCAHPS performance.
Sub-Section B – Literature Review on Merger Effect on Customer Satisfaction
Several studies have examined the impact of mergers on customer satisfaction. None of
these, however, includes analysis of hospital mergers on patient satisfaction. The general
conclusion from these studies of non-health care firms was that mergers have a negative
effect on customer satisfaction. One study found that customer satisfaction declined post-
merger primarily due to an over-emphasis on cost-cutting and efficiencies (Swaminathan,
Groening, Mittal, & Thomaz, 2013). Another report posited that customer satisfaction
declines were a result of the merged organization becoming internally focused, which
caused frontline employees’ concentration on customer service to decrease (Miles &
Rouse, 2011). The last analysis suggested that the merged organization did not give
employees enough time to adjust to the environment before post-merger changes were
implemented (Institute of Management and Administration, 2005).
Sub-Section C – Review of Research on Post-Merger Hospital Performance
The following review summarizes numerous studies of post-merger hospital
performance. The primary question motivating the research: How did the merger of two
hospitals or health systems impact performance? The common conceptual framework
applied in this research assumed the merged entity would have more financial resources
following the merger (due to better pricing and/or lower costs). Therefore, with additional
resources, the merged enterprise would be able to make certain investments in people,
systems, equipment, and facilities in order to improve operations and performance. The
objective of most of this research was to identify how hospital consolidation affected

performance compared to the pre-merger state. Some of the research sought to understand
why actual post-merger performance fell short of the pre-merger goals.
Many researchers focused on the impact of hospital mergers on quality from both
outcome and process standpoints. The general expectation was that quality would
improve post-merger by two mechanisms: (1) consolidation of certain complex services
(e.g., open heart surgery) into one facility, and (2) greater investments in
qualityenhancing activities and programs from the increased profits generated post-
merger (Birkmeyer, Stukel, & Siewers, 2002; Guerin-Calvert & Maki, 2014). However,
results from the 11 studies reviewed were equivocal. Most of the research conducted
found no statistically significant changes in quality post-merger (Bazzoli et al., 2004;
Gaynor &
Town, 2012; Romano & Balan, 2010; Universal Health Care Foundation of Connecticut,
2014). A few found a positive relationship between mergers and quality performance
(Cuellar & Gertler, 2005; Mutter, Romano, & Wong, 2011) while others found a negative
relationship (Encinosa & Bernard, 2005; Hayford, 2011).
Access-related comparative data are very limited (only two studies). Access was
defined in geographic terms and was measured by identifying one of two events: (1)
decision not to terminate a service that was slated for closure pre-merger, and (2) decision
to open a new service post-merger. Guerin-Calvert and Maki (2014) concluded that, in
aggregate, hospital mergers that occurred during the 20-year period studied (early 1990s
to early 2010s) had a slight favorable effect on preventing the shuttering of hospitals and
needed clinical services for at-risk, indigent, and rural populations. Several
researchers focused their merger analysis on internal efficiencies and cost reduction. For
example, mergers were shown to create a high potential for scale efficiency through the
elimination of duplication and the consolidation of services (Ferrier & Valdmanis, 2004;

Harris, Ozgen, & Ozcan, 2000; Harrison, 2011). Cost savings from technical efficiency
took longer to achieve but was still significant (Gross,
Lien, & Su, 2007). Most of these efficiency-examining studies compared the hospital’s
operating costs post-merger to the pre-merger levels. In the limited situations where the
merger generated efficiencies, the post-merger cost savings (computed by dividing total
operating costs by adjusted discharges) ranged from 2.5% to 14% with most of the
savings occurring in the first three years following the merger. After the initial, one-time,
merger-specific expense reductions were achieved, costs increased similar to other
hospitals (Ferrier & Valdmanis, 2004; Harris et al., 2000; Harrison, 2011; Noether &
May, 2017).
Extensive research on hundreds of hospital mergers, led by economist Dranove,
determined that the majority of hospital mergers did not result in decisions to consolidate
clinical services. Consolidating clinical services involves changes that may directly and
adversely affect key constituents including physicians and nurses. High levels of internal
resistance make it extremely difficult to implement clinical consolidation. Consequently,
most of the limited and temporary cost-savings are attributable to the ability of the larger
enterprise to consolidate administrative and support services (e.g., accounting, human
resources, marketing, information technology) and leverage its enhanced purchasing
power to negotiate lower input pricing for certain drugs and supplies (Dranove &
Lindrooth, 2003; Dranove & Shanley, 1995).
The most controversial findings related to the impact of mergers on pricing. Since
government pricing is fixed, these studies evaluated the prices paid by commercial payers
for inpatient services following a merger with their pre-merger levels. All but one of the
10 studies found a positive relationship between mergers and inpatient pricing (Gaynor &
Town, 2012). Nine of the 10 studies (Akosa, Gaynor, & Vogt, 2007; Dafny, 2009;

Dranove, Lindrooth, White, & Zwanziger, 2008; Haas-Wilson & Garmon, 2011; Melnick
& Keeler, 2007; Tenn, 2011; Thompson, 2011; Town, Wholey, Feldman, & Burns, 2006;
Wu, 2009) used regional data (i.e., limited to one or two states) while only one
comparison (Moriya, Vogt, & Gaynor, 2010) used national data. Inpatient prices
increased 20% to 45% on average immediately after the merger but leveled off after three
to five years. The merged entity was able to leverage its enhanced market power—
sometimes monopolistic power—to increase fees.
Higher inpatient prices charged to commercial payers can lead to higher insurance
premiums for employers. A study published in 2015, which analyzed insurance premiums
throughout California, found monthly premiums in highly concentrated hospital markets
were 8% higher compared to competitive markets (Thompson, 2015).
Another notable finding about a merger’s impact on inpatient pricing is that there
is generally no difference between for-profit (FP) hospitals and not-for-profit (NFP)
hospitals involved with a merger. Post-merger performance and conduct were identical
whether evaluating the consolidation of two FP or two NFP hospitals (Farrell, Pautler, &
Vita, 2009; Vita & Sacher, 2001).
One small study (merger of two hospitals) examined nurse reactions to hospital
consolidation (Armstrong-Stassen, Cameron, Mantler, & Horsburgh, 2001). The study
was based upon previous research conducted by Cartwright (1997) that analyzed
employee responses to mergers across many industries, which identified high levels of
post-merger stress and dissatisfaction. Armstrong-Stassen et al. (2001) found a
statistically significant decrease in job satisfaction among nurses during the first two
years following the merger.
Perhaps the most comprehensive meta-analysis of hospital mergers was performed
by Bazzoli, Dynan, Burns, and Yap (2004). These researchers reviewed 38 merger-related

empirical research studies conducted over a 16-year time period. Bazzoli et al. applied a
conceptual model of organizational change based on four dimensions of change: content,
process, context, and outcomes. The authors concluded that most hospital mergers were
largely motivated by financial, strategic, and operational factors and primarily pursued to
increase market power, lower costs, and protect profitability. Merging organizations, in
general, did not fully consider, estimate, or place a high importance on psychological
costs (human factors) associated with consolidation. The human toll and resistance
originating from internal structures and relationships were commonly overlooked.
Consequently, estimates on the net impact of the merger (i.e., projected merger benefit –
projected merger cost = net impact) under-estimated the merger-related costs by not
appreciating the human factors and negative effects associated with the social
phenomenon. Essentially, the merger’s projected net impact
was over-estimated and overstated.
Sub-Section D – Review of Research on the Post-Merger Disruption Effect
There is a substantial body of quantitative and qualitative research identifying,
examining, and explaining the post-merger disruption effect. Marks and Mirvis (1985)
were the first researchers to formally label the social phenomena as the “merger
syndrome” (p. 50). This syndrome encompasses the various aspects of the “culture clash”
associated with the blending of two organizations (Marks & Mirvis, 1992, p. 19). The
symptoms of the syndrome include preoccupation by senior management with internal
power struggles, poor communication to frontline employees, decreased morale,
increased turnover, confusion, resistance to change, personal stress and anxiety,
uncertainty, active and passive conflict, and deteriorating organizational performance
(e.g., revenues not hitting forecasts, higher expenses, falling productivity, declining
profits, quality issues, customer complaints) (Altendorf, 1986; Meeks, 1977; Sinetar,

1981). The short-term consequence of this phenomenon is that the organization’s
attention turns inward in an effort to resolve syndrome-related problems and restore
organizational performance (Marks, 1994; Marks & Mirvis, 1985, 1997; Mirvis & Marks,
1992).
In an effort to view and understand the post-merger environment from an
individual perspective, Shaw (2002) incorporated elements of Hofstede’s (1991)
sixdimensional culture classification model and Stuart’s (1995) personal journey map into
a survey of individual employees involved with the merger of two British hospitals. This
approach provided insights into the various stages or “terrains across which individuals
make their change journey” (Shaw, 2002, p. 218). Although not every person in a
postmerger integration experiences all terrains, the general pathway includes the
following:
• sensing,
• worry work,
• positioning,
• shock,
• hoping and sharing,
• holding on,
• letting go,
• moving, and
• moving on and moving away.
Employees described personal feelings in the post-merger environment by using terms
such as emotional distress, deep pain, sad, tearful, unsettling, resentment, anger, despair,
grief, and negative (Shaw, 2002).
Cartwright and Cooper (1993) examined post-merger disruption at the middle
manager level. Middle managers play an important role in any organization since they (a)
frequently serve as a key intermediary between senior management and frontline
workers; (b) exert significant influence on the job satisfaction and overall perceptions of

their employees; and (c) are oftentimes the group of employees most adversely affected
by merger-related restructuring, consolidation, and rationalization plans.
Research by Cartwright and Cooper involved surveys of 157 middle managers
following the merger of two large professional service organizations (building societies in
England). The two organizations were considered highly culturally compatible prior to
merger based on results from an independent review and a cultural survey of employees.
The two societies served a similar customer base and performed similar services.
However, despite these apparent pre-merger cultural advantages, there was a substantial
level of disruption in the post-merger environment. Cartwright and Cooper used a
questionnaire of middle managers to gain insights into the underlying problems and
source of post-merger disruption.
One set of questions measured stress and mental health using two standardized
scales (Free Floating Anxiety and Hysterical Personality). The survey revealed high
levels of stress and fear among middle managers one year following the merger. These
managers revealed their reluctance to express anxiety believing that it could jeopardize
their career opportunities. The merger appeared initially and overtly to be progressing
well; however, the covert and pernicious effects were occurring beneath the surface
(Cartwright & Cooper, 1993).
Not all mergers trigger or result in the same level of post-merger disruption. Poor
cultural fit between two organizations is a critical factor in post-merger integration and
human resource problems. Cultural differences in the post-merger environment result in
misunderstandings, clashes, conflict, tension, emotional reactions, infighting, and
disruption (Hambrick & Cannella, 1993; Nahavandi & Malekzedah, 1988; Weber &
Schweiger, 1992). Weber’s exploratory research (1996), which focused on 73
acquirertarget mergers in the same industry (homogenous operations with similar

products and a common market of customers), sought to isolate, operationalize, and
measure certain variables (i.e., characteristics) of the two top management teams (TMT),
which are key components of cultural fit.
Weber (1996) hypothesized that the “greater cultural differences between the
combining top management teams, the lower the effectiveness of the integration process
and the lower the financial performance of the buying firm” (p. 1185). Controlling for
several organizational and merger characteristics, Weber found: (a) cultural differences
among TMTs were negatively associated with the effectiveness of the integration process
in acquirer-target situations, and (b) the effectiveness of the integration process affected
post-merger organizational performance and shareholder value (Weber, 1996).
Overall Synthesis of the Literature Review’s Sub-Sections A, B, C, & D
Providing a positive patient experience is a top priority for hospitals. How patients
perceive their inpatient care episode directly influences HCAHPS ratings and patient
preference/loyalty. Reimbursement from CMS and other payors is affected by
HCAHPS performance; therefore, a hospital’s financial well-being is linked to its patient
experience performance. Patient perceptions of inpatient care are predominantly
influenced by their interactions with physicians, nurses, and other staff. The working
environment and overall job satisfaction of physicians, nurses, and staff directly
influences the patient experience and a hospital’s HCAHPS ratings. It is nearly
impossible to deliver a positive patient experience when the key individuals responsible
for creating that experience (physicians, nurses, and general staff) are distracted,
frustrated, anxious, stressed, unhappy, disgruntled, or angry.
Hospital mergers are substantially motivated by a desire to achieve greater scale,
increase market power, and improve financial performance. Scale can be leveraged to
protect or increase pricing. Scale can also be utilized to achieve certain internal operating

efficiencies. In general, hospital mergers do not result in lower hospital fees or health
insurance premiums for the markets served. In most cases, prices and premiums increase
at a higher rate post-merger compared to similar hospitals that did not merge. Viewed as a
whole, merged hospitals do not outperform non-merged hospitals in terms of quality,
safety, and access.
Significant, internal disruptions occur following most mergers. Successfully
blending two organizations is delayed or hampered by culture conflict and TMT clashes.
Organizational performance can be adversely and temporarily affected by this postmerger
disruption effect as resources and attention are focused inward to address and resolve the
social disturbance.
Conceptual Framework
Most efforts to effect significant organizational change fail to meet expectations
(Burke, 2002; Probst & Raisch, 2005). Organizational change-related research, conducted
over a 30-year period involving numerous industries, found that 50% to 70% of major
change initiatives do not achieve their intended goals (Beer & Nohria, 2000; Sturdy &
Gray, 2003). Overall organizational performance oftentimes declines in the near-term
aftermath of core organizational change (March, 1981; Mellert, Scherbaum, Oliveira, &
Wilke, 2015). Significant organizational change also increases the potential for
organizational death (Singh, House, & Tucker, 1986).
Mergers represent a radical change in an organization’s structure, ownership,
governance, and strategic direction (Peus, Frey, Gerkhardt, Fischer, & Traut-Mattausch,
2008). Most mergers—across all industries, time periods and nations—either fail or fall
substantially short of achieving their intended goals (Bergh, 1997; Gugler & Yurtoglu,
2008; Montgomery & Wilson, 1986; Ravenscraft & Scherer, 1987, 1989; Tichy, 2001).
Additionally, Carper (1990) found a negative relationship between mergers and

shareholder wealth. Finally, in a meta-analysis of mergers and acquisitions (M&A), King,
Dalton, Daily, & Covin (2004) found post-M&A financial performance did not improve
and, on average, performance declined.
The U.S. health care industry, including the hospital sector, is no exception to the
challenges associated with mergers. Extensive research has been conducted examining
the impact of hospital mergers on various outcome variables including quality, safety,
access, service development, and expansion, pricing, internal operating costs, and
profitability. The general conclusions from this large body of empirical research suggest
that most hospital mergers do not achieve their intended operational or financial goals, do
not increase shareholder value (for-profit hospitals), and do not enhance consumer/public
welfare (Bazzoli et al., 2004; Gaynor, 2011; Gaynor & Town, 2012; Town et al., 2006).
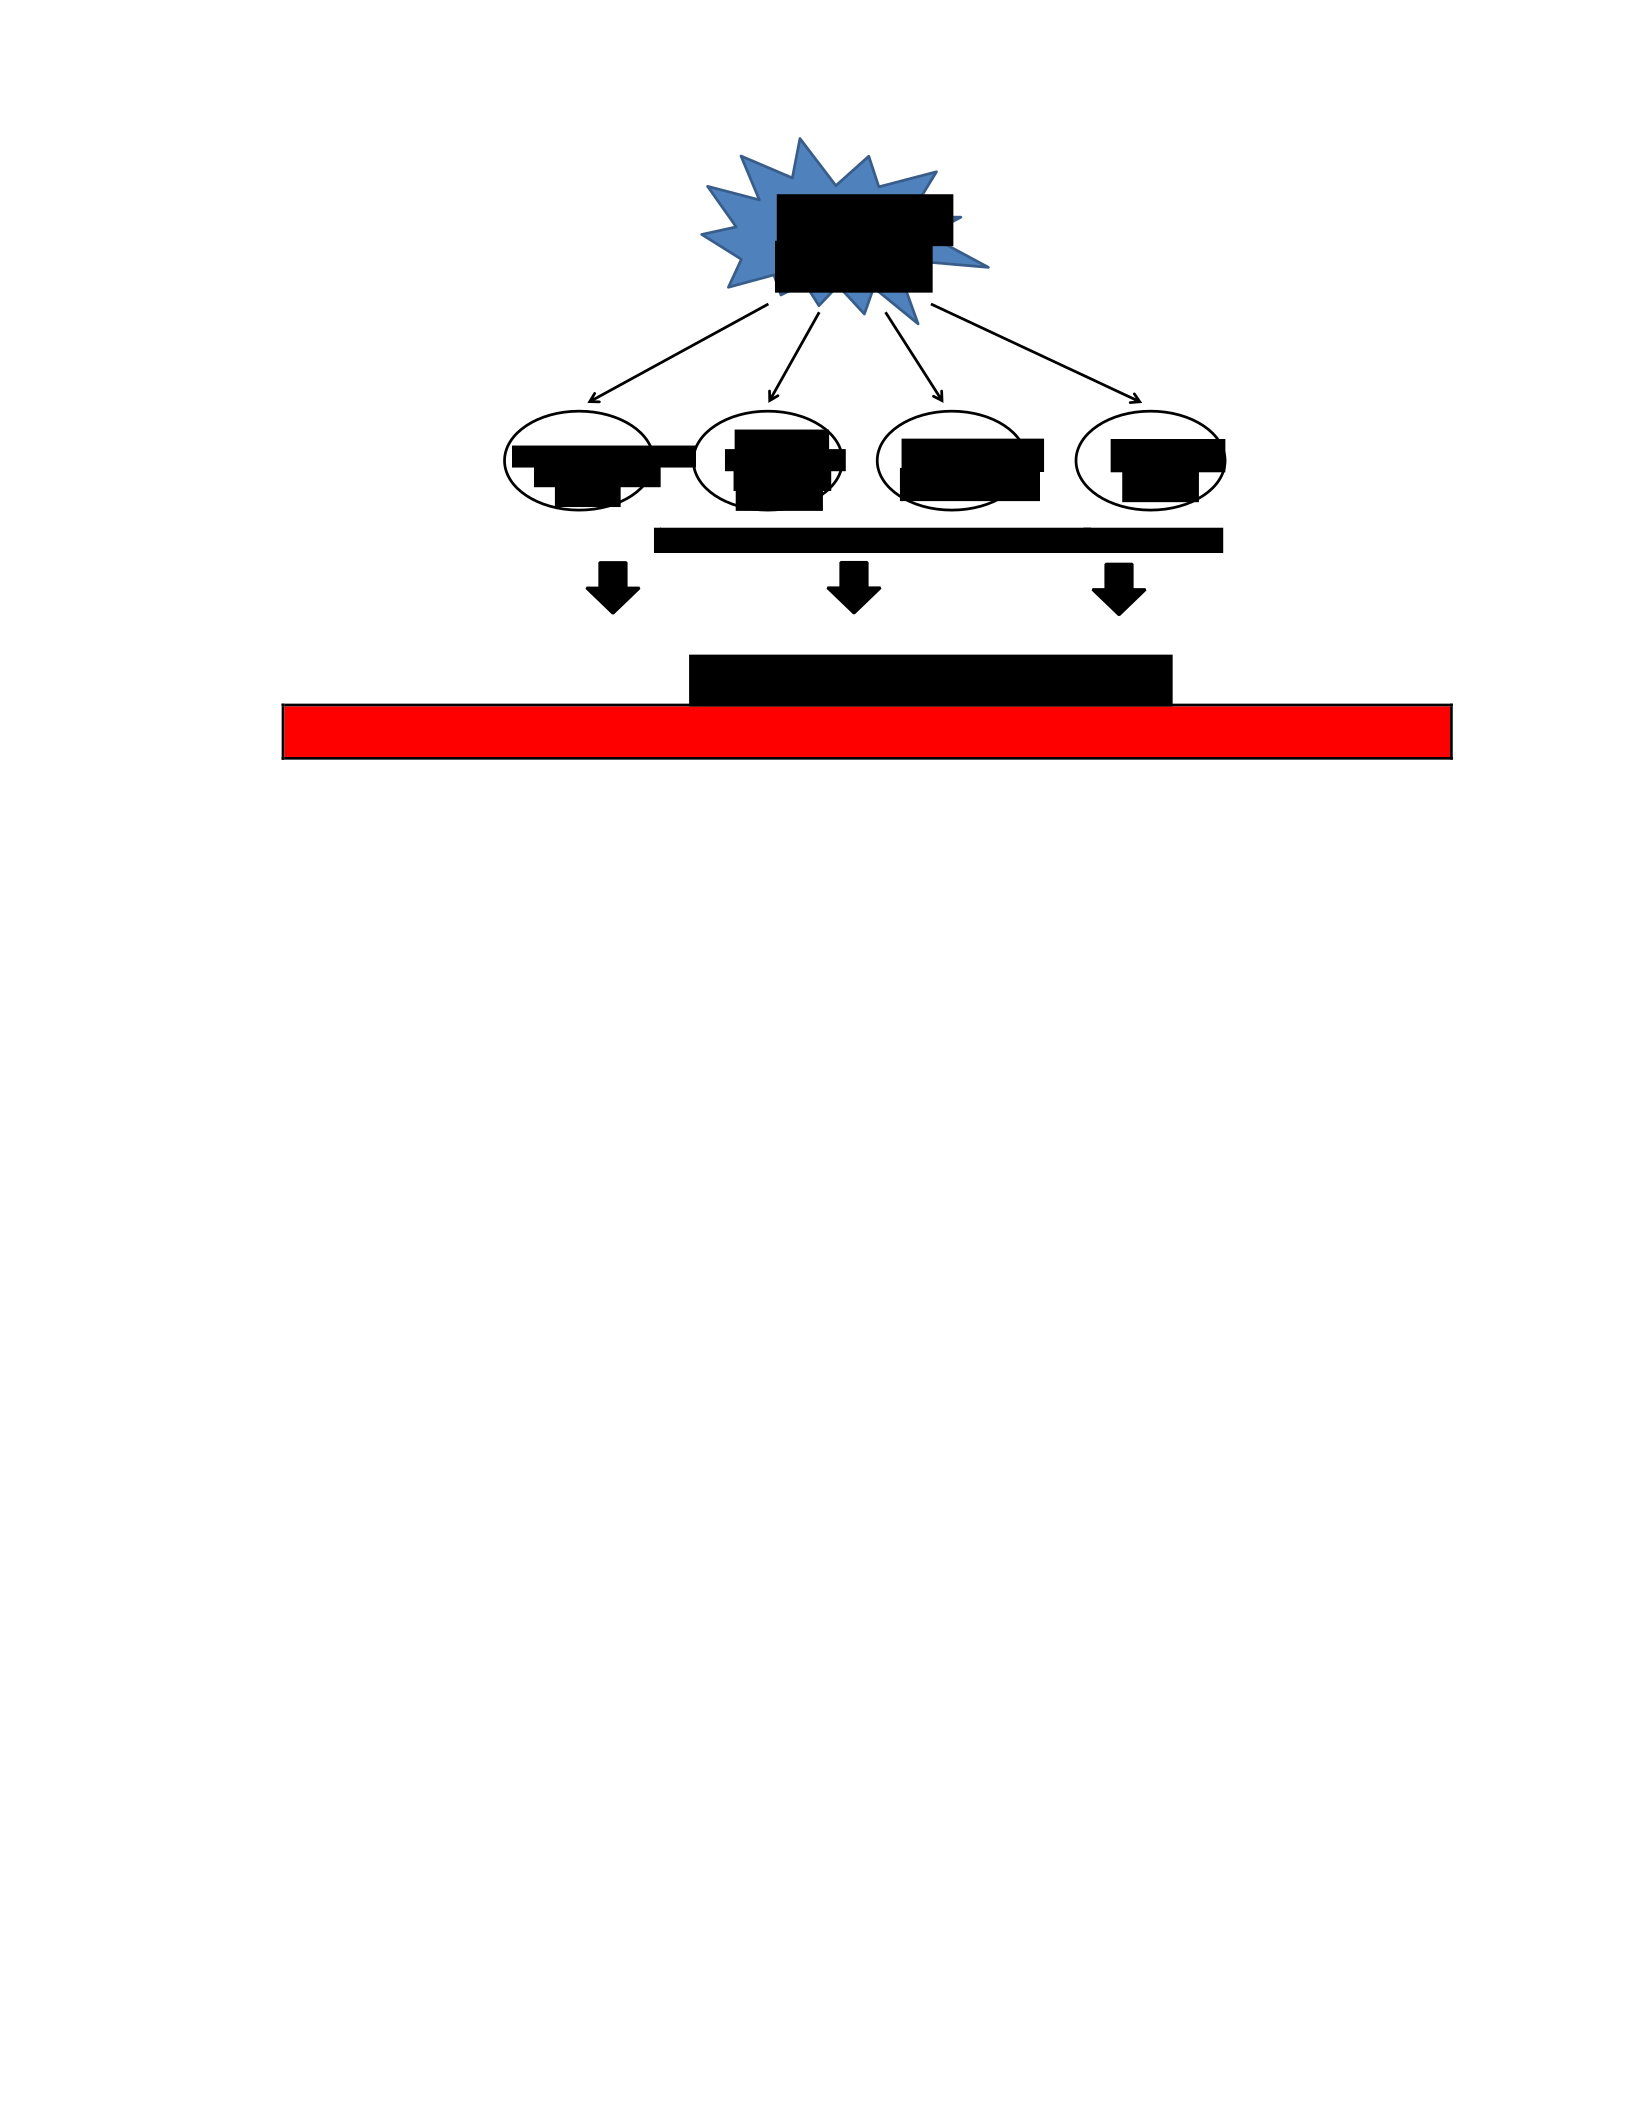
Figure 4 and Figure 5 provide graphical presentations of the conceptual
framework developed for this research of hospital mergers and their impact on patient
experience. This framework depicts the relationships and social phenomena this study
examined. Figure 4 reflects the general mechanism associated with core, structural, or
second-order organizational change. Numerous research studies on radical change and
mergers identified and analyzed these phenomena (Carroll & Harrison, 2004; Haveman,
1992; Morgeson, Mitchell, & Liu, 2015; Pritchett, 1987; Weber & Camerer, 2003; Zell,
2003). How merging organizations address people and cultural integration directly
influences productivity, efficiency, quality, retention rates, and customer service (Bogen
& Symmers, 2001).
ORGANIZATIONAL PERFORMANCE
Figure 4. General mechanism associated with core, structural, or second-order
organizational change.
Figure 5 combines the concepts associated with core organizational change with
merger-related disruptive effects applicable to the multi-hospital merger situation.
Starting in the upper left corner, hospital or multi-hospital system A merges with hospital
or multi-hospital system B, resulting in multi-hospital system C. The merger is motivated
by offensive (proactive) and/or defensive (reactive) desires, goals, and forces. In addition
to significant investments of time and money, the pre-merger process involves various
strategic, financial, economic, operational, technological, legal, regulatory, governance
and political analyses, issues, and hurdles.
Once those hurdles are addressed, hospital/system A and hospital/system B merge,
becoming system C. Despite the wide-ranging pre-merger planning and preparatory work,
internal issues arise post-merger. Following the formal start of the merged entity’s
operations (Time 0 in Figure 5), system C experiences certain disruptive effects due to the
integration and blending of the two organizations. These cultural and human factor
effects, which will be discussed in Section Two, collectively cause an overall disturbance
Disruptive Effect on
Operations &
Culture
Employee
Resistance &
Emotional
Response
Conflict &
Alienation
Internal
Focus
Radical
Change
NEGATIVE IMPACT ON
(
distraction, decreased morale, and increased turnover
)

in system C’s internal operations. Consistent with findings by Bogen and Symmers
(2001), this social phenomenon, in turn, may adversely impact system C’s
organizational performance and stakeholder value creation.
One important measure of a hospital’s performance is patient satisfaction.
Therefore, a reasonable postulate based on this conceptual framework is that system C’s
patient experience performance will initially decline as a direct result of the mergerrelated
social phenomena and its disruptive effects.
Over time (shown in Figure 5 as three years post-merger or Time +3), the social
issues are fully resolved or, if not, the merger fails (the merger is dissolved with system A
and system B resuming independent operations). Assuming the disruptive effects are
resolved, system C’s operations enter a state of equilibrium as shown in Figure 5. The
focus shifts back to external value creation and, consequently, organizational performance
improves or is restored as measured by the various elements at the bottom of
Figure 5.
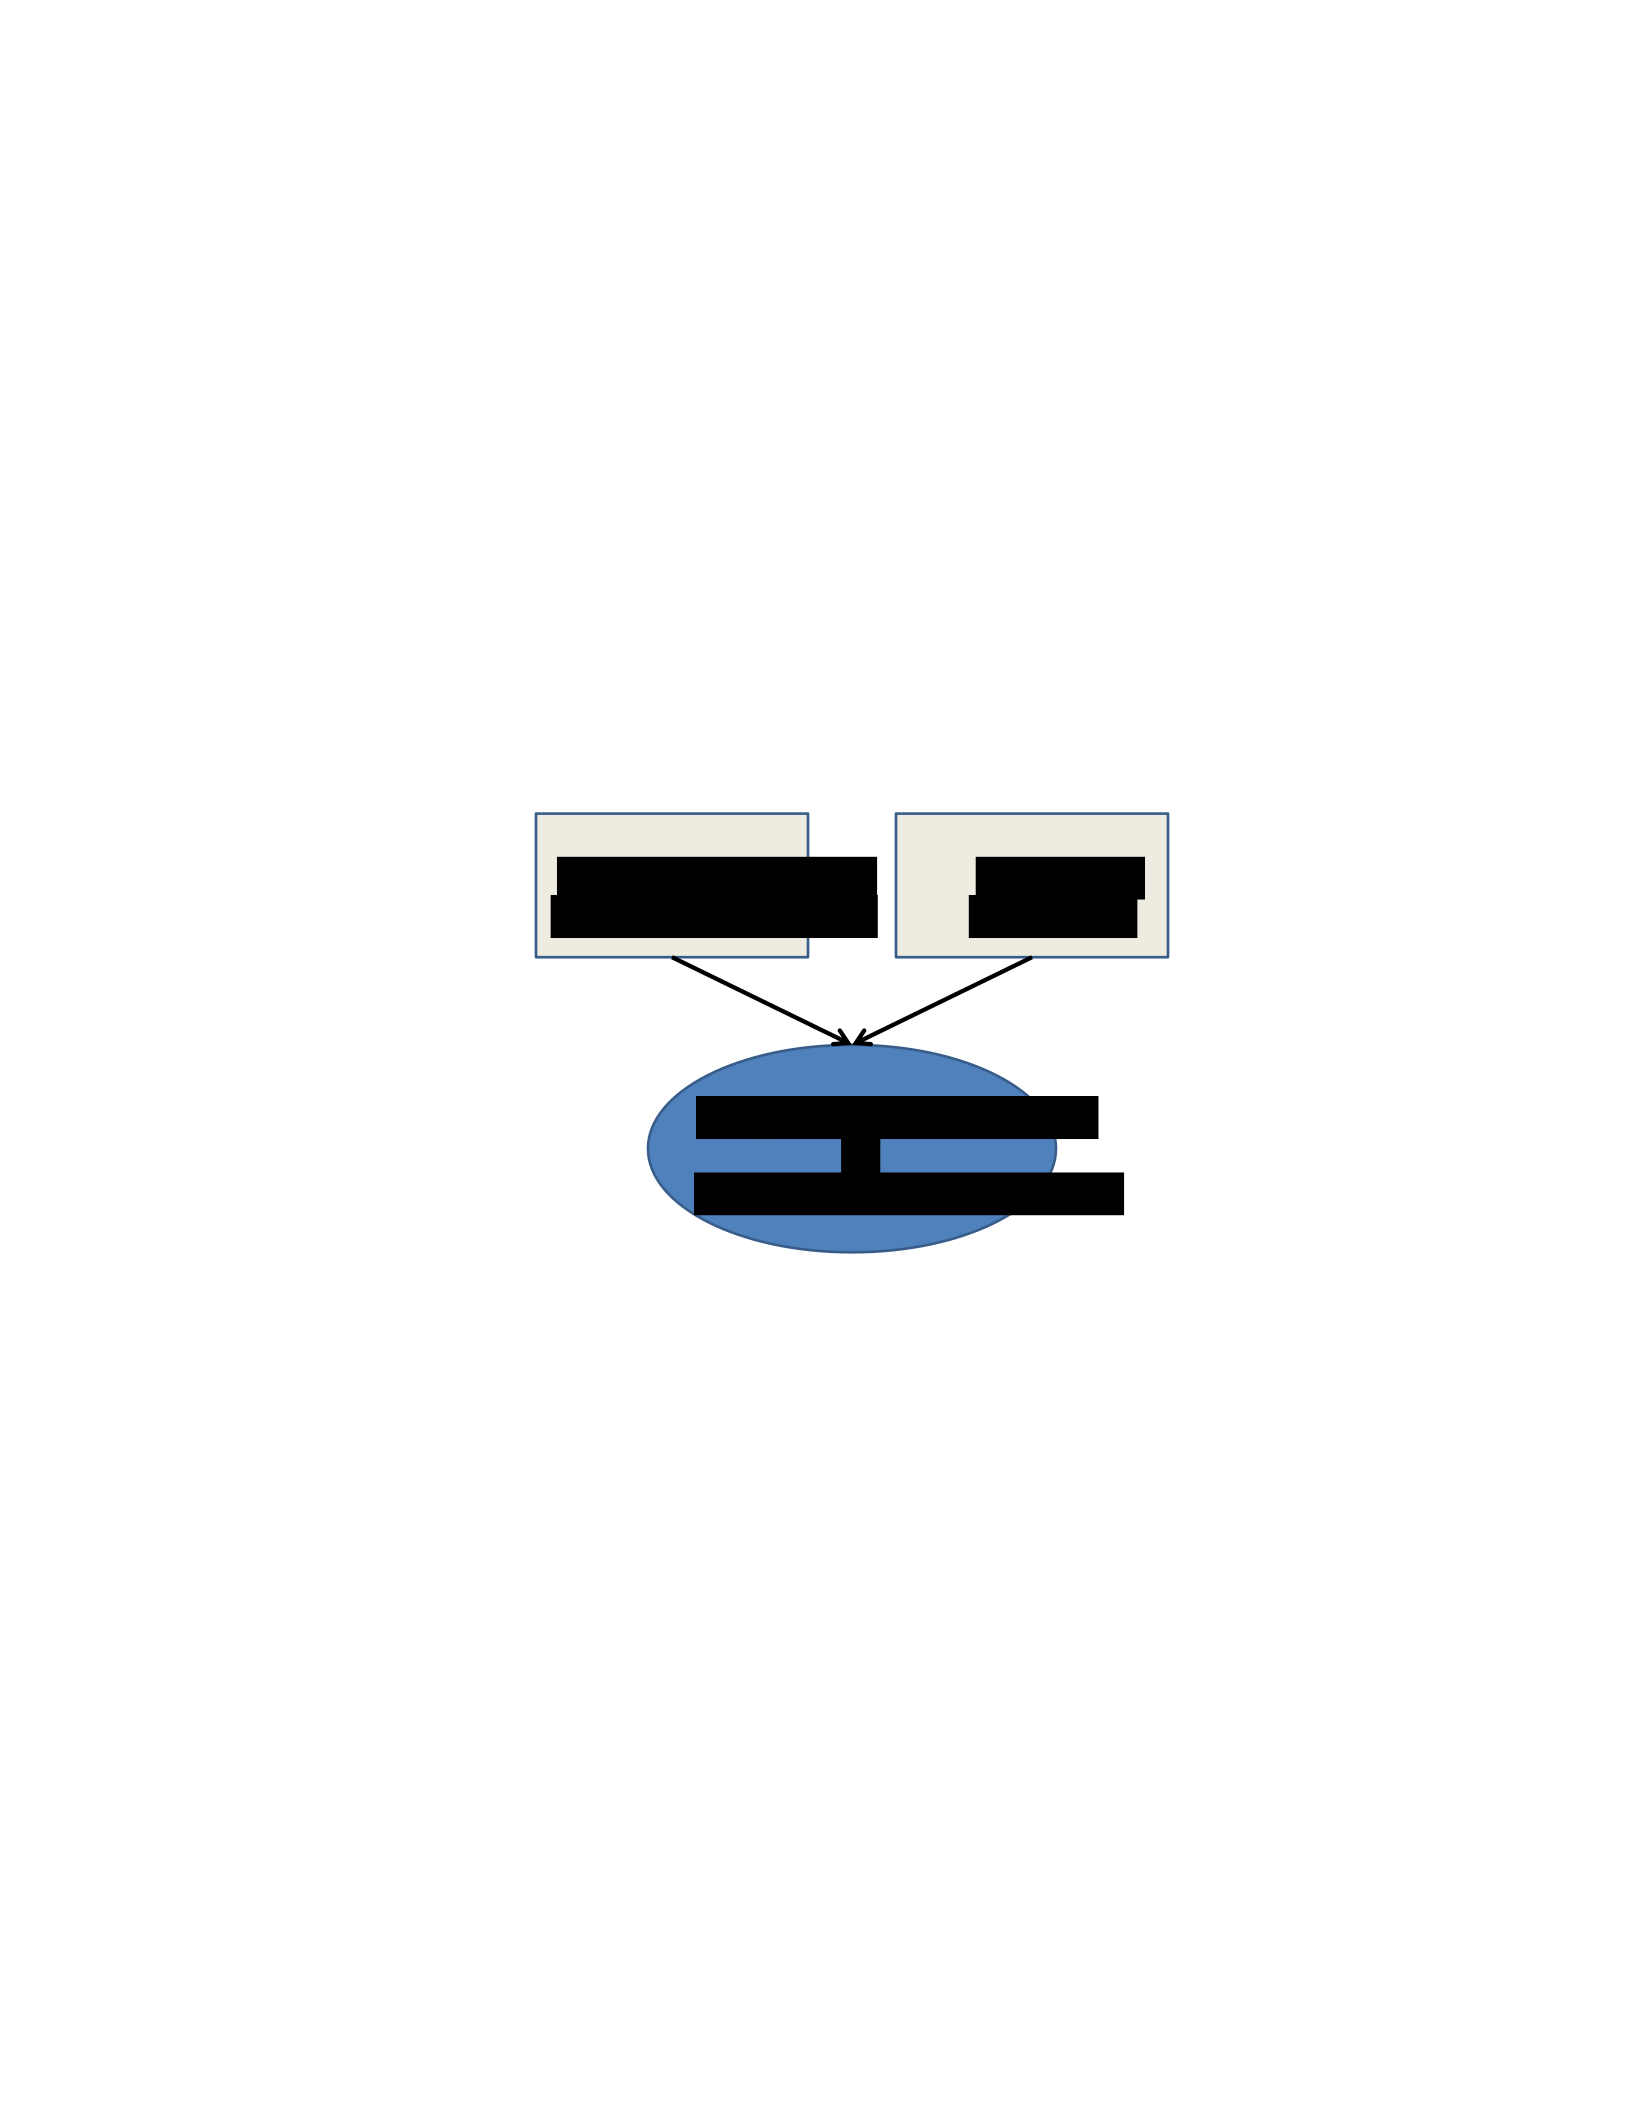
Figure 5. Organizational change and merger-related disruption effects.
Pertinent Theories
There are two broad categories of organizational behavior theories (see Figure 6)
applicable to this research: (1) organizational change related theories, and (2) merger
related theories. Each category contains several specific theories that explain the
relationships and general impact mechanisms depicted in the proposed conceptual
framework (see Figures 4 and 5). Two pertinent, specific theories (one theory from each
of the two broad categories) were selected to support this research.
PERTINENT THEORIES
Figure 6. Pertinent theories including organizational change theories and merger theories.
Organizational Change: Structural Inertia Theory
Organizational change has several definitions. The definition developed by Huber,
Sutcliffe, Miller, and Glick (1993) supports the conceptual framework discussed in
Section One. The authors defined the phenomenon as “[c]hange that involves differences
in how an organization functions, who its members and leaders are, what form it takes,
and how it allocates resources” (p. 216). In 1995, Van de Ven and Poole defined
organizational change as a difference in form, quality, or state. Health systems and health
ORGANIZATIONAL
CHANGE THEORIES
MERGER
THEORIES
P
-
M Disruption
&
D Pe

care organizations are under pressure to become more efficient, improve coordination,
take on more risk for clinical performance, and enhance service to patients (Bazzoli et al.,
2004). To address these challenges health care enterprises are changing, sometimes in
radical and discontinuous ways (Shortell, Gillies, Anderson, Mitchell, &
Morgan, 1993).
The organizational change-related theories emanate from comprehensive research
examining how and why organizational change occurs, how employees respond, how
change efforts affect performance, how change efforts often fail, and other factors.
Structural Inertia Theory (SIT) was applied in this study to support the conceptual
framework and hypotheses.
SIT is one theory among a group of organizational change theories labeled as
selection theories (Barnett & Carroll, 1995). Barnett and Carroll classified change
theories into two groups: (1) strategic adaptation theories, and (2) selection theories. The
first group, strategic adaptation theories, explains organizational change as a response to
market and technological pressures with the change progressing in harmony with the
external environment thus leading to positive results and market affirmation. In contrast,
selection theories suggest that organizations “cannot easily change and face substantial
risks when they do” (Bazzoli et al., 2004, p. 252).
Mellert et al. (2015) applied SIT, along with other change theories, in research on
the effectiveness of organizational change initiatives and the impact on financial
performance. Mellert and colleagues (2015) found substantial evidence to support SIT.
There is a high risk of failure associated with organizational change, particularly change
in core structure. Singh et al. (1986) also found that core organizational change increases
the probability of organizational death. In general, employees at all levels of the
organization resist change and respond negatively to change efforts (structural inertia)
(Peus et al., 2008).

The magnitude of change is an important correlate of change commitment: the
more the change impacts organizational operations, the larger the resistance (Fedor,
Caldwell, & Herold, 2006). Internal elements in the organization (e.g., authority
structures, culture, routines) serve as passive or active deterrents to change (Peus et al.,
2008). These phenomena are amplified in merger and acquisition situations. A merger is a
special form of core organizational change and typically results in greater internal
resistance and disruptive effects (Cloodt, Hagedoorn, & van Kranenburg, 2006; Correia,
Cunha, & Scholten, 2013).
In previous research applying SIT, Haveman (1992) found that core organizational
changes (e.g., change in strategic direction, merger, acquisition) reset the
“liability-of-newness clock” (Stinchcombe, 1965, p. 143). The organization must
establish new routines, learn new patterns of communication, build new flows of
information, and integrate new members. Immediately following the implementation of
radical change, the “organization diverts a considerable portion of its resources from
operating to restructuring” (Haveman, 1992, p. 51). In other words, the organization
becomes more inwardly focused and less focused on its customers. Consequently,
operating efficiency declines which is followed by lower performance.
Morgeson et al. (2015) examined organizations as a composition of events within
an industry comprised of a broad pattern of environmental events. The authors
categorized events using three parameters: novelty, disruption, and criticality. All events
have some level of strength (impact), space (origin and scope of impact within the
organization), and time (duration). Merger events are highly novel, disruptive, and
critical. Mergers have high impact, affect all levels of an organization, and have a long
duration (two to three years or longer). Mergers may be a shock, jolt, and turning point
for an organization and are described as a discontinuous, non-routine, and discrepant

event. Consequently, a lingering period of internal confusion, uncertainty, disturbance,
and instability may follow a merger. Disruptive events, such as mergers, shake people out
of their routine thinking, behavior, and response modes. These changes affect all levels of
the organization including the individual, team, department, and business unit. Finally,
the bigger the event, the more time it may take the organization to fully absorb the
changes and return to a state of equilibrium, stability and normalcy (Morgeson et al.,
2015).
Zell’s research (2003) on organizational change applied Kubler-Ross’s (1969) five
stages of grief to understand resistance to major change within professional
bureaucracies. Zell defined professional bureaucracy as “an organization consisting of
highly trained and autonomous professionals such as hospitals and universities” (p. 73).
Mintzberg (1983) identified special dynamics in professional bureaucracies that uniquely
affected organizational change. Resistance to change is higher, the pace of change is
slower, and the success rate of sustainable change is significantly lower (Mintzberg,
1983).
Merton’s (1957) research on bureaucracies and change identified two
dysfunctions related to organizational inertia: (a) bureaucracies are excessively rigid in
their application of rules and regulations, which limits their ability to change; and (b)
bureaucracies are “inherently conservative and resistant to innovation” (p. 48). Physicians
and nurses are members of professional societies and enjoy varying levels of
independence in their practice. Successful and sustainable change in a professional
bureaucracy is highly contingent upon the active support of professional staff. Active or
passive resistance to change by members of the professional bureaucracy creates more
upheaval, emotional turmoil, conflict, and disruption. Due to the special characteristics of
the professional bureaucracy, Zell observed that the final Kubler-Ross stage (acceptance)

may not occur until two to three years following the commencement of the change
process (Zell, 2003).
Merger-Related: Culture Conflict Theory
Several merger-related theories have been developed by economists,
organizational behavior scientists, sociologists, and psychologists to answer one
overarching question: Why do most mergers fail or substantially fall short of their
intended goals? Culture conflict has been found to be the principal culprit. Merger
research has discovered a unique set of behavior factors that affect and shape the
postmerger environment. Human actors’ behavior affects, and is affected by, the distinct
and temporary dynamics that occur post-merger. Certain patterns in this organizational
behavior have been observed and categorized. Culture Conflict Theory (CCT) was used
to explain the social phenomena and support the conceptual framework.
Developed by Weber and Camerer in 2003, CCT is an extension of prior,
mergerrelated empirical research involving culture conflict. Weber and Camerer
conducted laboratory experiments of human subjects in a simulated merger situation and
discovered prospective partners significantly underestimated or ignored cultural hurdles
during the pre-merger due diligence period. Weber and Camerer posited that culture is
rooted in shared meaning and shared meaning is based on common language, beliefs, and
understanding. Study results supported research hypotheses. Performance of the
simulated merger operations was adversely affected by culture conflict among human
subjects (compared to pre-merger performance). Culture conflict was observed and
measured using standardized metrics.
Weber and Camerer constructed a merger-specific culture conflict theory that
includes the following broad components: (a) culture conflict can be mitigated and
potentially avoided if the parties to a merger take appropriate precautions in advance; (b)

culture conflict leads to post-merger performance deterioration; (c) even when the
potential for culture conflict is acknowledged, participants in the experiment significantly
underestimated the performance decline that would occur; and (d) individuals are more
likely than not to assign blame for culture conflict to employees from the other
organization than take responsibility for their contributions to the conflict (Weber &
Camerer, 2003).
CCT is an extension of a large body of research on organizational culture as both
a dependent and independent variable (Deal & Kennedy, 2000; Kilmann, Saxton, &
Serpa, 1985; Kotter & Heskett, 1992; Schein, 1992). Mergers involve acculturation, the
blending of two organizations’ cultures (Carroll & Harrison, 2004). Nahavandi and
Malekzadeh (1988) developed a conceptual framework with four modes of successful
post-merger acculturation: (1) preservation (both parties maintain their existing cultures),
(2) symbiotic (intentional efforts to combine the best cultural elements of the two
organizations), (3) absorption (only the culture of the dominant organization is
maintained), and (4) transformation (a completely new culture is established). Many
organizational culture researchers suggest that acculturation is the single most important
predictor of post-merger success (Carroll & Harrison, 2004; Ellis & Lamont, 2004;
Larsson & Finkelstein, 1999).
Carroll and Harrison (2004) provided insight on the roles culture and
acculturation play in post-merger performance. Evidence showed that the most effective
and expeditious method for resolving post-merger culture conflict consisted of two steps:
(a) clearly establish and communicate the norms and values that define the culture of the
merged entity, and (b) use alienation tactics as a way to achieve conformity or elimination
of those who decide not to conform. This method works best in acquirertarget situations
where a larger entity acquires or takes over a smaller organization (Carroll & Harrison,
2004).

CCT is further supported by research conducted by Allred, Boal, and Holstein
(2005). The authors initially set out to examine why there was such a high failure rate for
mergers. Allred and colleagues found that economic logic, financial factors, and
economic performance post-merger did not explain the failure rate. After evaluating
numerous variables Allred et al. (2005) hypothesized that human integration and
interaction factors were the dominant contributors to merger failures.
Furthermore, the authors noted a close psychological parallel between the
dynamics involved with the merging of two step-families and the integration of two
merged organizations. In a remarriage situation, the two partners’ needs are the focus
often without regard to the needs of the children (Lampard & Peggs, 1999). Allred et al.
(2005) identified three stepfamily models that explain the relationship problems that often
occur: (1) biological discrimination (stress between the stepparent and stepchildren); (2)
incomplete institutionalization (greater stress post-merger combined with a lack of
common rules, which leads to a perception of insiders and outsiders); and
(3) the deficit-comparison (employees from the dominant organization in the merger will
have greater job security and resource allocation compared to employees of the subordinate
organization).
Relatedness and relative size between the two merging organizations may also
limit and influence the level of culture conflict. There are two unique merger types
subject to the related and relative size influence. The first is when a large firm acquires a
small firm (i.e., a takeover or acquirer-target situation). In this case, employees and
managers of the small firm may feel unimportant and trivialized by the buyer. This leads
to feelings of alienation and discontent among the small firm staff. Culture conflict is
limited to the small firm since the culture of the large, acquiring firm is imposed upon the
target firm’s operations (Weber, 1996).

The second situation in which relatedness and relative size moderates culture
conflict is in a full merger-of-equals (MOE) situation involving firms of similar size
operating in the same industry. In this case the two firms are rivals; they know each other
well and have overlapping geographic market areas. There is no acquirer or target and no
clear winner or loser. As a result, MOEs intensify culture conflict with TMT power
struggles, surfacing of hidden agendas, board control clashes, policy disputes, and
political infighting (Devine, Lamont, & Harris, 2016; Lodorfos & Boateng, 2006).
Acculturation is severely impaired by this environment, which results in internal turmoil
and suboptimal organization performance until the culture conflict issues are resolved
(McEntire & Bentley, 1996).
Post-merger culture conflict varies by the type(s) of organizations involved.
Culture conflict may be lower when two manufacturing firms consolidate (Weber, 1996)
and more intense, with a longer duration, within the service industry (Bond & Weisman,
(1997). Among service industry firms, the hospital and health system environment may
be the most challenging of all (Bruhn, 2001).
Composite: Structural Inertia Theory Plus Culture Conflict Theory
The composite theoretical framework is shown in Figure 3. These two theories
(SIT and CCT) provide the supporting empirical research and conceptual foundation for
the primary impact mechanism of interest to this research: significant and predictable
social disruptions directly cause a temporary decrease in post-merger organizational
performance. In other words, post-merger performance is inversely related to the level of
disruption that occurs so that higher disruption equals lower performance.
The disruptive effect is a social phenomenon. People at all levels of authority and
seniority in the merging organizations frequently respond and react in negative ways.
They passively or actively resist change. There is an increase in stress, confusion, fear,

uncertainty, anxiety, betrayal, and feelings of isolation. Job satisfaction and job security
levels decline. Cultural conflict exacerbates the intensity and duration of the disruption.
Human energy and efforts are distracted and inwardly focused. Consequently,
organizational performance is often adversely affected until the integration and social
issues are fully resolved. Eventually, the merged organization achieves equilibrium and
resumes stable operations.
The disruptive effect and resistance may be worse in a hospital setting due to the
entrenched professional bureaucracies of physicians and nurses (Bond & Weisman, 1997;
Zell, 2003). Organizational change is difficult. Mergers, as a radical form of
organizational change, are extremely challenging and risky. Of all business and industry
environments, the unique context of a merger in a hospital or health care system setting
may be the most perplexing organizational change situation (Bruhn, 2001).
Combining the post-merger research with the two pertinent theories further
illuminates, and provides a compelling reinforcement for, the conceptual framework. The
study of hospital mergers, including an examination of the factors that led to the merger
decision and the merged entity’s post-merger performance, reveals several interesting
points. First, the pre-merger activity is primarily focused on the various technical tasks
required to consummate the transaction (i.e., legal, regulatory, financial due diligence).
Second, little, if any, attention is given to the soft or human components of the merger.
Third, senior leadership of the surviving entity initially focuses their post-merger
operations management and strategic execution on maximizing the merged entity’s
market power (i.e., optimize reimbursement from commercial payers and negotiate lower
input pricing). Fourth, the social phenomenon and the various disruptive effects begin to
manifest themselves soon after the merger. Fifth, it takes two to three years following the
merger for the merger disruption effects to fully dissipate.

Statement of 12 Hypotheses
It is expected that post-merger disruption will adversely impact a recently merged
hospital’s overall performance. One measure of a hospital’s performance is patient
experience. Consistent with the literature review, conceptual framework, SIT, and CCT, a
hospital’s patient experience performance will decline in the near-term following a
merger:
Hypothesis 1: A hospital’s overall patient experience ratings will be negatively
associated with having recently completed a merger (within the last 12-24
months). Compared to similar hospitals that did not merge, recently merged
hospitals’ year-over-year change in overall patient experience ratings will be
lower.
Post-merger disruption is a social phenomenon that affects human behavior and
individuals’ emotional and mental states. Patient experience performance is directly
influenced by the attitudes and behaviors of key employees including physicians, nurses,
and other staff. The post-merger disruption effect manifests itself by increased
anxiety/stress, increased turnover, and decreased job satisfaction among employees. A
hospital’s HCAHPS composite scores among each of the three human interaction
domains (physician communication, nurse communication, and staff responsiveness) will
be adversely affected as a consequence of the post-merger disruption.
Hypothesis 2a: A hospital’s physician communications ratings will be negatively
associated with having recently completed a merger (within the last 12-24
months). As a group, recently merged hospitals’ year-over-year change in
physician communications ratings will be lower compared to the physician
communications ratings for similar hospitals that did not merge.

Hypothesis 2b: A hospital’s nurse communications ratings will be negatively
associated with having recently completed a merger (within the last 12-24
months). As a group, recently merged hospitals’ year-over-year change in nurse
communications ratings will be lower compared to the nurse communications
ratings of similar hospitals that did not merge.
Hypothesis 2c: A hospital’s staff responsiveness ratings will be negatively
associated with having recently completed a merger (within the last 12-24
months). As a group, recently merged hospitals’ year-over-year change in staff
responsiveness ratings will be lower compared to the staff responsiveness ratings
of similar hospitals that did not merge.
As discussed previously in this chapter, culture conflict and the merger-related
disruption effect are oftentimes greater and more difficult to resolve in the MOE situation
versus an acquisition.
Hypothesis 3a: Compared to the subgroup of Acquired hospitals, the subgroup of
MOE hospitals will have a lower, year-over-over change in overall patient
experience ratings. In other words, the MOE hospitals subgroup will have a
bigger negative comparative difference in overall patient experience ratings
versus the Acquired hospitals subgroup.
Hypothesis 3b: Compared to the subgroup of Acquired hospitals, the subgroup of
MOE hospitals will have a lower, year-over-year change in physician
communications ratings. In other words, the MOE hospitals subgroup will have a
bigger negative comparative difference in physician communications ratings
versus the Acquired hospitals subgroup.
Hypothesis 3c: Compared to the subgroup of Acquired hospitals, the subgroup of
MOE hospitals will have a lower, year-over-year change in nurse communications

ratings. In other words, the MOE hospitals subgroup will have a bigger negative
comparative difference in nurse communications ratings versus the Acquired
hospitals subgroup.
Hypothesis 3d: Compared to the subgroup of Acquired hospitals, the subgroup of
MOE hospitals will have a lower, year-over-year change in staff responsiveness
ratings. In other words, the MOE hospitals subgroup will have a bigger negative
comparative difference in staff responsiveness ratings versus the Acquired
hospitals subgroup.
Merger disruption is a temporary phenomenon. Based on a vast body of
postmerger research, there is general agreement that the merged operation will, in most
cases, achieve cultural equilibrium and resume normal operations within three years
following the merger. Performance declines, attributable to the disruption effect, will be
reversed. Hypothesis 4a: Merged hospitals’ overall patient experience ratings will return
to normal levels within 36 months post-merger with no performance difference compared
to similar hospitals that did not merge.
In the long-term, the post-merger disruption effect that negatively impacted
physicians, nurses, and other employees will be fully resolved. The merged hospital’s
HCAHPS composite scores among each of the three human interaction domains
(physician communication, nurse communication, and staff responsiveness) will return to
normal levels.
Hypothesis 4b: There will be no difference in physician communications ratings
between merged and similar unmerged hospitals three years following the merger.
Hypothesis 4c: There will be no difference in nurse communications ratings
between merged and similar unmerged hospitals three years following the merger.
Hypothesis 4d: There will be no difference in staff responsiveness ratings
between merged and similar unmerged hospitals three years following the merger.

CHAPTER 3
METHODOLOGY
Chapter 3 describes the research methodology. First, the general research design
is described followed by a definition and explanation of the measures for the dependent
and independent variables. Second, the process is explained for identifying the merged
and unmerged/matched hospitals. Third, data sources for each variable are presented. The
chapter concludes with a summary of the statistical testing that was conducted for each of
the 12 hypotheses.
Research Design
The purpose of this research was to examine the relationship between hospital
mergers and patient experience. Hospitals were the subjects of this study. Consistent with
other hospital consolidation and closure research (Farrell et al., 2009; Ona, Hudoyo, &
Freshwater, 2007; Sinay & Campbell, 2002), this study used a retrospective,
quasiexperimental design of merged hospitals (intervention group or the “Event
hospitals”) compared to unmerged hospitals (synthetic control group or the counterfactual
“Matched
Hospitals”). For purposes of this study, “intervention” will refer to a merger between two
or more hospitals.
Since patient experience was measured both pre- and post-merger, with three
measures for both pre- and post-periods, the design meets the definition of an interrupted
time series study (AHRQ Taxonomy for Defining a Research Design, Appendix C).
Measures

Dependent Variables – Patient Experience Scores
The dependent variables for this study were four HCAHPS composite ratings (see
Appendix B for the complete set of HCAHPS survey questions):
(a) Overall patient experience (Question 21), hereafter referred to as “OVERALL”.
The percentage of patients who rated their overall patient experience as a “9” or a “10”,
on a scale of 0 to 10);
(b) Nurse communication (Questions 1, 2, and 3), hereafter referred to as “NURSE
domain.” The percentage of patients who responded “always” (among the four
response options: “never,” “sometimes,” “usually,” and “always”). These
percentages were averaged across the three nurse communication questions to
create a composite NURSE domain variable;
(c) Physician communication (Questions 5, 6, and 7), hereafter referred to as
“PHYSICIAN domain.” The percentage of patients who responded “always” (among the
four response options: “never,” “sometimes,” “usually,” and “always”). These
percentages were then averaged across the three physician communication questions to
create a composite PHYSICIAN domain variable;
(d) Staff responsiveness (Questions 4 and 11), hereafter referred to as “STAFF
domain.” The percentage of patients who responded “always” (among the four
response options: “never,” “sometimes,” “usually,” and “always”). These
percentages were then averaged across the two staff communication questions to
create a composite of the
STAFF domain variable.
HCAHPS measurements (Figure 7) from six 12-month periods were obtained for
each Event hospital and Matched hospital: “T1” corresponded with the period three years
prior to merger, “T2” corresponded with the period two years prior to merger, “T3”
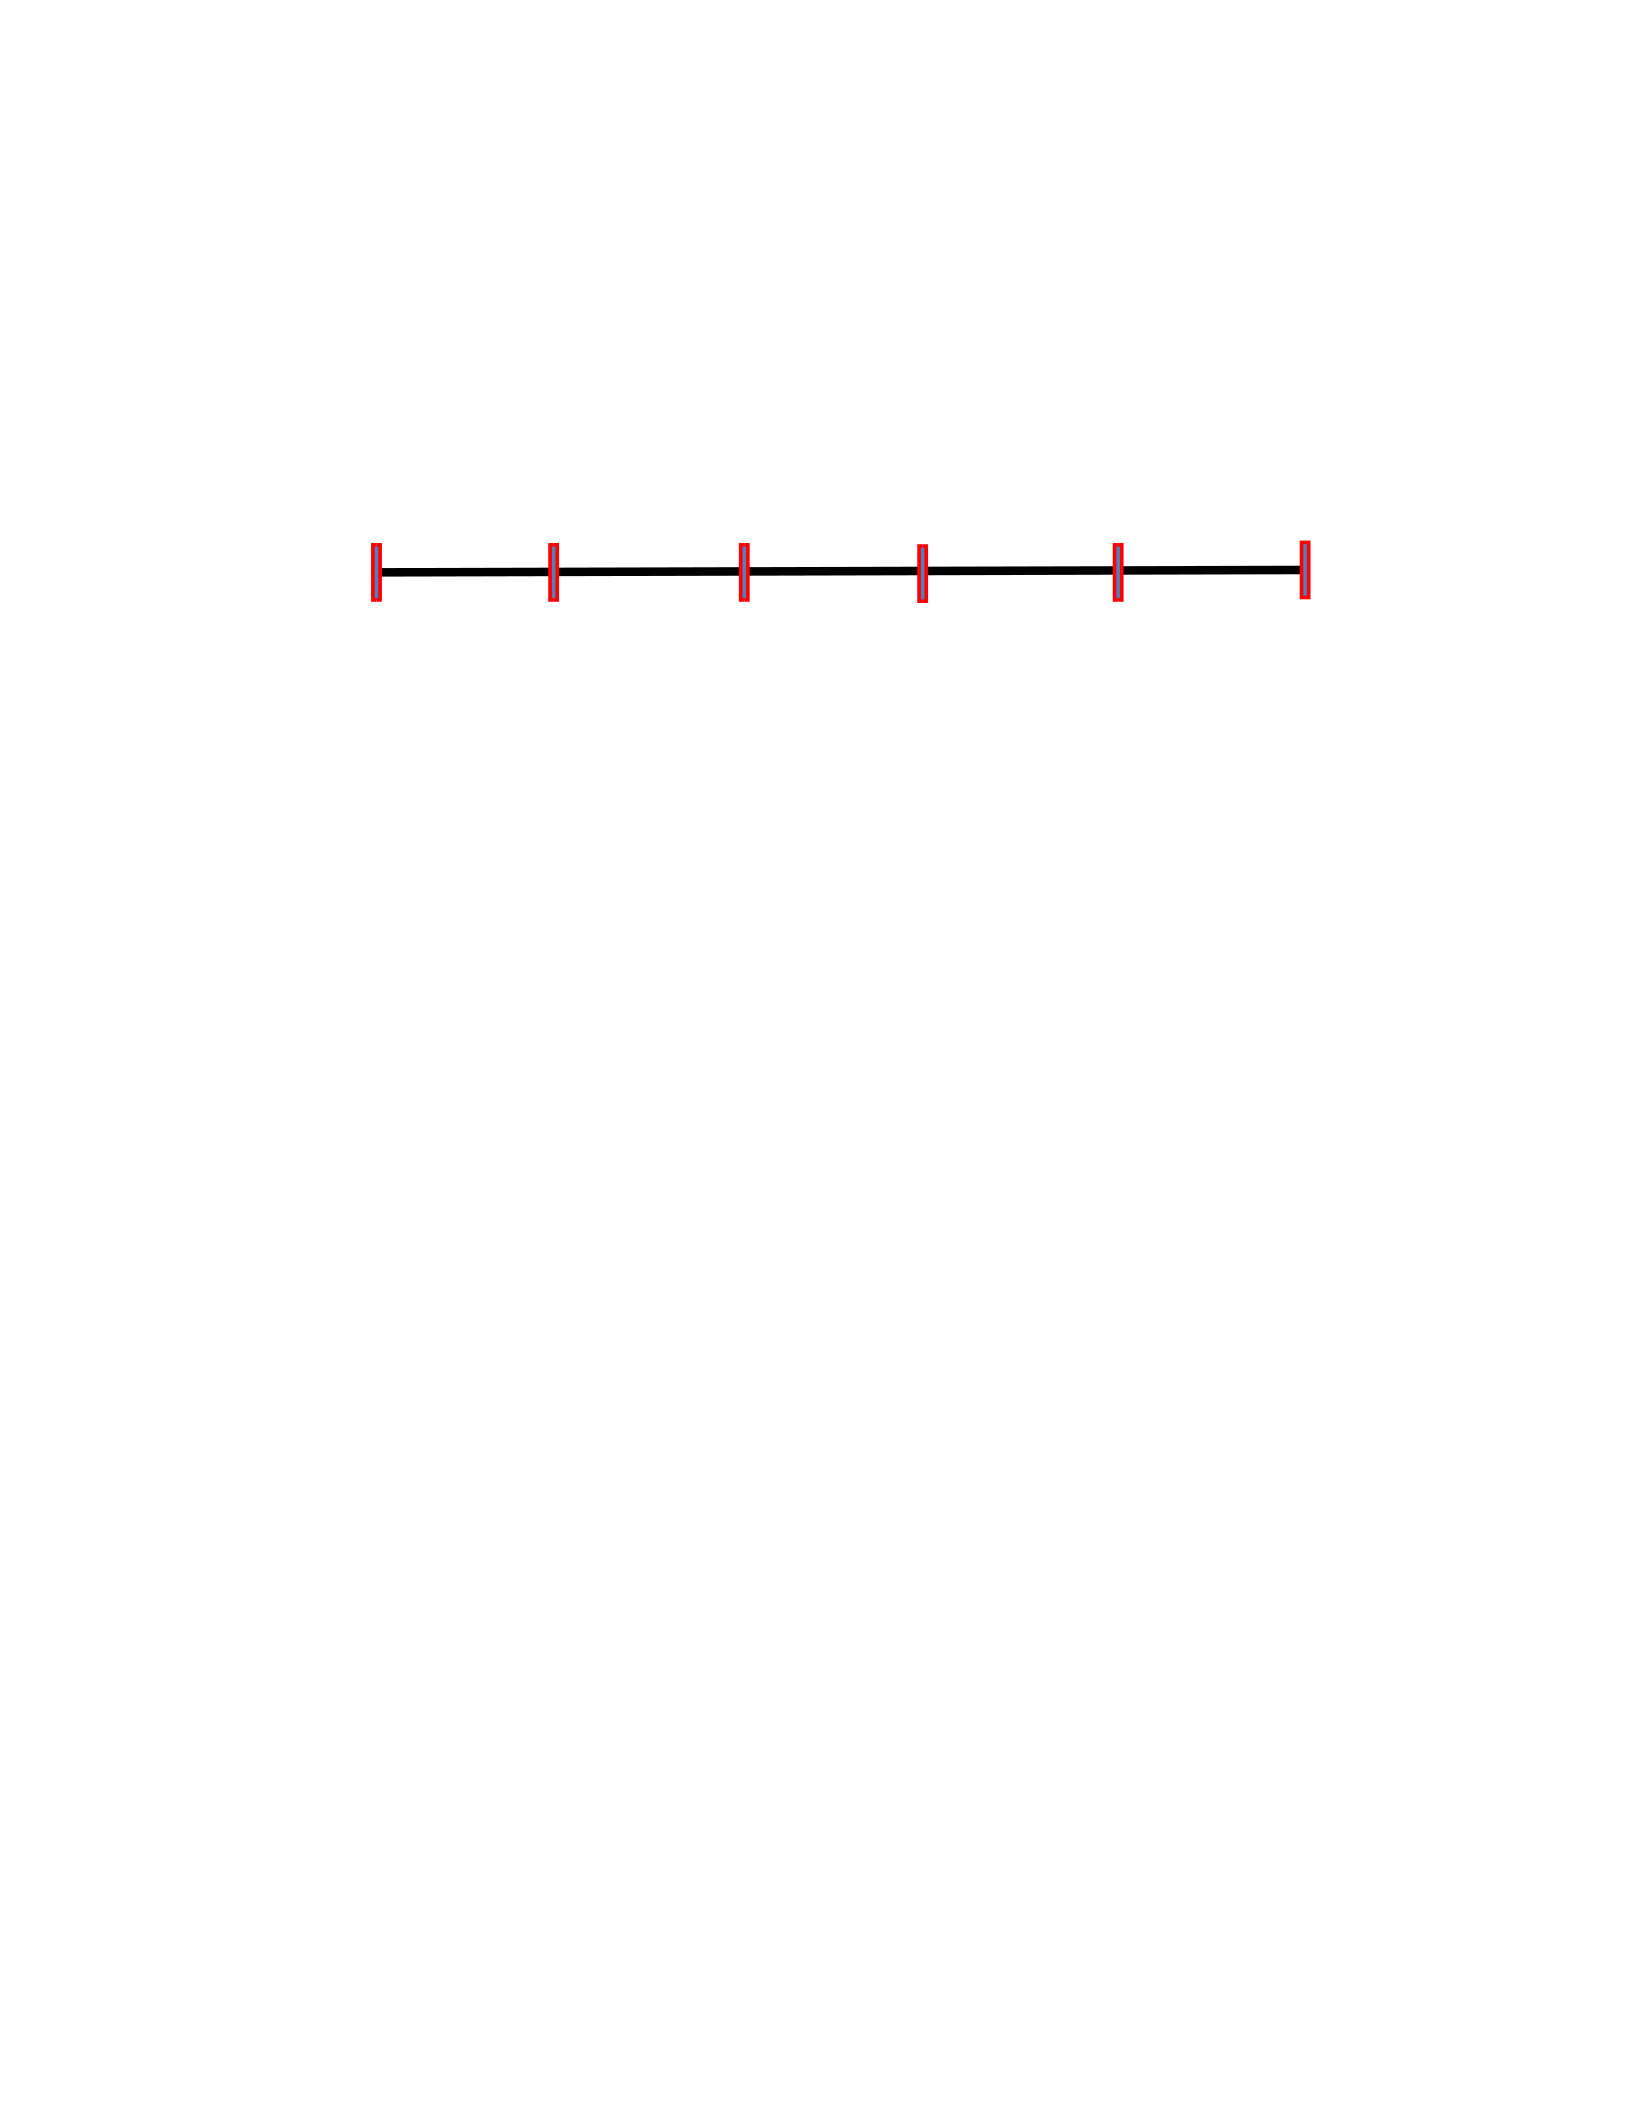
corresponded with the period one year prior to merger, “T4” corresponded with the period
one year following merger, “T5” corresponded with the period two years following
merger, and “T6” corresponded with the period three years following the merger year.
Time Span of the Six Year-Ending HCAHPS Measures
T1 T2 T3 T4 T5 T6
25-36 Months 13-24 Months 1-12 Months 1-12 Months 13-24 Months 25-36 Months Pre-Merger Pre-Merger Pre-Merger Post-Merger
Post-Merger Post-Merger
Figure 7. Time span of the six HCAHPS measures.
Independent Variable – Merged or Unmerged
The independent variable for this study was a dummy variable that reflected the
merger status of a hospital: “event” hospital (hospital that was part of a merger or was
acquired) (1) or unmerged or “matched” hospital (0). The following sections provide the
working definition that was used to identify the Event hospitals and the matching
approach that was utilized to identify the Matched hospitals.
Rationale for the Six Measures and the Timing of Each
The first three measures (T1, T2 and T3) provide a snapshot of the “pre-event”
status. These three measures reflect an Event hospital’s annual HCAHPS performance
levels prior to the potential impact of merger-related disruption effects. The last three
measures (T4, T5 and T6) provide the post-merger HCAHPS performance: one year post,
two years post, and three years post. Applying the theoretical basis concerning merger
disruptions, the hypothesized, adverse impact on HCAHPS performance will manifest
itself within the first 12 to 24 months following the merger event (T4 and T5). The final
measure (taken three years following the merger event) reflects the HCAHPS
performance beyond the merger disruptive effects. In other words, the final measure (T6

in Figure 7) reflects HCAHPS performance after the full resolution of the disruption
effects (i.e., the hospital has resumed normal operations).
Three years post-merger was selected based on several research studies in which
researchers suggested that it takes two to three years for the organizational change and
merger-related negative effects to dissipate (Bazzoli et al., 2004; Habeck, Kroger, &
Tram, 2000; Lim, 2014; Zell, 2003). Individual years were selected in order to detect any
temporal effects, trends and differences for each of the years leading up to the merger
event and for each of the years following the merger event. Looking at a composite rating
for all three years prior to the event (composite of T1, T2 and T3 in one HCAHPS rating)
or post-event could mask a temporal trend. For example, if HCAHPS performance among
the Event hospitals significantly declined in comparison to the Matched hospitals in only
one of the three post-merger years, a single post-merger composite rating (combining T4,
T5 and T6 into one value) would, possibly, mask that performance difference.
Study Population – Inclusion and Exclusion Criteria
Definition of Event Hospitals
The population of Event hospitals consisted of U.S.-based acute care hospitals
(ACH), excluding federal government-owned/operated and Indian Health Service
hospitals, that were part of a merger transaction that closed during the five-year time
period of January 1, 2009 through December 31, 2013. An “Event” was defined as a
transaction between two or more ACHs, or health systems owning/operating two or more
ACHs, involving the combining or consolidation of those hospitals’ operations into one
surviving organization (i.e., one single tax identification number entity) that has one
governing body and one common management team.
This type of organizational consolidation can occur through a Merger-of-Equals
(MOE) or Acquisition. The following working definition was used for an MOE (adapted

from Georgieff & Latsky, 2018, page 61; DePhamphilis, 2014, pages 412-413):
a transaction consisting of two organizations of generally similarly sizes (primarily
using most recent year-end operating revenue to determine size),
• there was no designated “acquirer”,
• post-merger, the two legacy organizations formed a new entity with a
new name and new governance structure (i.e., neither of the two
legacy system’s names survived), and
• all assets held by the two legacy organizations were placed under the
control of the new entity and its governance.
Conversely, an Acquisition transaction involves one larger organization
purchasing the assets or stock of a smaller organization with the larger organization’s
name and governance surviving the transaction. Post-transaction, all of the assets of the
acquired entity are under the control of the acquiring entity. A dummy variable was
created for “merger type” with each Event hospital categorized as an MOE (1) or
Acquisition (0).
The following multi-hospital consolidation transactions were excluded from the
sample: ACHs that entered into other forms of ACH-to-ACH or health system-to-health
system relationships (e.g., joint ventures, partial ownership interests, affiliations, shared
service agreements, contract management); ACHs acquired through bankruptcy
proceedings; merged or acquired ACHs that terminated operations during the study
period; and ACHs that completed one merger followed by another merger or
consolidation transaction within the 2009-2013 time period.
Although the MOE or Acquisition results in a consolidated operation with one tax
identification number entity owning the merged or acquired ACHs, in the vast majority of
cases, each merged ACH continues to operate under its own National Provider Identifier

(NPI). Since each ACH is required by CMS to report its individual HCAHPS survey
results, HCAHPS ratings continued to be available for each merging ACH.
Identifying the Study’s Event Hospitals
Irving Levin Associates (ILA) compiles and publishes an annual report containing
the pending, announced and completed hospital mergers and acquisitions during the
preceding calendar year. To evaluate the status of ILA as a source for hospital mergers
and acquisitions, a literature search, limited to items published between 2000 and 2017,
was conducted using the following key words: “hospital” + “merger” + “Levin.” Over
1,000 published articles and reports were identified, which reference the ILA reports at
their source for hospital merger and acquisition activity. In addition, queries were
submitted to Modern Healthcare, Dixon Hughes Goodman, Becker’s Hospital Review,
and Kaufman-Hall seeking sources of information for tracking hospital mergers in the
United States. All the individuals contacted use the ILA report exclusively. Therefore,
The ILA Hospital Acquisition reports for 2006 through 2016 (11 calendar years) were
purchased. These reports served as the source for identifying the qualifying ACHs that
merged.
The first step involved identifying all qualifying transactions announced during
the five-year time period, 2009 through 2013. This transaction period was chosen to allow
for three-year pre- and post-merger periods of evaluation. Based on the review of the ILA
reports, 381 ACHs were part of a Merger-of-Equals (MOE) or Acquisition announcement
from January 1, 2009 through December 31, 2013 (collectively referred to as “Event”
hospitals). Figure 8 provides a graphical summary of the overall identification and
matching process resulting in the final set of 99 pairs (198 hospitals) for this study.
NOTE: For purposes of this study, all the ACHs involved in an MOE were
included but only the target hospital (i.e., the hospital being acquired) was counted in the

Acquisition event category. The rationale for not including all the acquiring entity’s
hospitals is based upon the theoretical framework and empirical research on the
potentially disruptive effects of mergers and acquisitions. In an MOE situation, both
legacy organizations are subject to the substantial change and social upheaval associated
the blending of the two organizations (Devine, Lamont, & Harris, 2016; Lodorfos &
Boateng, 2006). In an Acquisition situation, the larger, acquiring organization remains
operationally and culturally intact while the “target” organization (for this study, the
hospital that was purchased), potentially, experiences significant change and disruption as
it transitions into a new governance and management structure, new name, new policies
and procedures, and new culture.
The next step involved determining whether each of the pending, announced, or
proposed transactions was consummated. Following the initial listing of a proposed
transaction, the ILA reports did not consistently include a subsequent entry for closed
transactions or previously proposed deals that did not close. Therefore, in addition to the
ILA reports, other sources and methods were used to ascertain the final status for each of
the proposed transactions. Those sources included Modern Healthcare, Becker’s Hospital
Review, and regional newspapers and business periodicals. Finally, in some cases, none of
the published sources contained conclusive information about the final status of a
proposed transaction originally recorded in ILA. In these cases, a Google search was
conducted using a combination of the following key words: name of hospital(s), merged
(or acquired), closed, final and approved.
After applying all sources and methods for verifying which transactions closed,
164 hospitals were eliminated. In all 164 cases, the initially proposed MOE or
Acquisition failed to materialize for a variety of reasons, including one or both parties to
the deal deciding not to pursue the merger, community backlash, medical staff backlash,

disapproval or a threatened challenge from state or federal authorities, lack of financial
resources, or other factors. Of the originally identified 381 hospitals, 217 hospitals
completed the MOE or Acquisition transaction (381 - 164 = 217). When each MOE or
Acquisition was confirmed, the month and year of the transaction’s closing was recorded.
The final step involved applying the previously described inclusion and exclusion
criteria. For example, if a hospital was acquired in 2009 by one health system and the
acquiring health system merged with another health system in 2011, that hospital was
excluded from the study. If a merged or acquired hospital closed within the three-year
period following the transaction, it was excluded. Thirty-eight hospitals were removed
after applying the inclusion and exclusion criteria. A total of 179 acute care hospitals
remained in the study’s population (217 - 38 = 179).
Building the Profile for Each MOE or Acquired Hospital
In preparation for matching, a comprehensive profile was constructed for each of
the 179 hospitals. The AHA Annual Survey was used as the primary source. The year of
the transaction determined which AHA Annual Survey year to use. For example, if an
MOE occurred in 2009, the MOE hospital’s profile was completed using data from the
2009 AHA Annual Survey. The following 10 data points were obtained and recorded
from the AHA reports:
a. hospital name and address,
b. AHA identification number,
c. Medicare certification number,
d. National Provider identification number,
e. geographic area (name of the CBSA or the word “rural” if the hospital was
not located in a defined CBSA),
f. number of licensed beds (continuous variable),

g. annual admissions (continuous variable),
h. annual adjusted admissions (continuous variable),
i. system status (categorical, dummy variable), and
j. profit status (categorical, dummy variable).
In approximately 25% of cases, the NPI number was not included in the AHA Annual
Survey. An alternative source was identified and used to obtain all the missing NPI
numbers (www.NPInumberlookup.org).
Matched Hospitals
Hospitals in the Matched hospital group were identified using pre-determined
matching variables (see next section, Matching Approach). The goal was a 1:1 ratio of
Matched hospitals and Event hospitals with no hospital serving as a match more than
once. All Matched hospitals were part of a multi-hospital system or a single hospital
operation that did not experience a merger event during the same time period (20092013).
Consistent with the theoretical framework, the Matched hospital group excluded hospitals
that were part of a merger or acquisition (including a hospital or health system that
acquired another hospital or health system) that occurred three years prior or three years
after the corresponding Event hospital’s transaction year. This was done to avoid overlap
with the disruptive effects of a merger within the Matched hospital group.
Matching Approach
The methods used for selecting the Matched hospitals were critical components of
the study. Hospital performance is significantly affected by local and regional factors
such as demographics, population growth or decline, economic conditions,
reimbursement rates, payor mix, state Medicaid expansion, presence of certificate-ofneed,
social issues, and more. The goal was to find the ACH that most closely resembled each
merged ACH.

The matching process involved two sequentially applied methods: (1) an
automated approach using Propensity Scoring Matching with greedy matching (PSM),
and (2) manual matching. PSM was conducted first followed by manual matching.
Manual matching was necessary since some of the Event hospitals were not located in a
defined CBSA and since PSM was limited to “within the same CBSA” hospitals.
Initial Matching Using PSM
A hierarchical PSM was used for the initial identification of a Matched hospital
for each of the Event hospitals. PSM used the following categories of matching
covariates: (1) geographic match by name of the Core Based Statistical Area (CBSA) (see
Appendix A for the U.S. map of CBSAs), and (2) size match using licensed beds,
admissions and adjusted admissions. The year of the Event hospital’s transaction
determined which year of AHA Annual Survey to utilize for the matching covariates. For
example, if a hospital was acquired in 2010, PSM utilized data from the 2010 edition of
the AHA Annual Survey for PSM matching.
PSM provided a preliminary match for 152 of the 179 Event hospitals. Several of
the 27 “unmatched” Event hospitals were located outside of a defined CBSA (i.e.,
hospitals located in rural areas). In these cases, the PSM method was unable to locate a
nearby geographic match.
Manual Matching
Following the output of PSM, a manual or non-automated matching approach was
used. This involved a case-by-case review of all hospitals located within the Event
hospital’s CBSA, adjacent CBSA, or nearby rural county (for Event hospitals located
outside of a defined CBSA). Appendix D contains a summary of the manual matching
algorithm. Of the 27 “unmatched” instances from PSM, manual matching located 20

acceptable matches. In total, there were 172 hospitals with preliminary matches, resulting
in the elimination of seven of the 179 Event hospitals.
Examination and Testing of the 172 Preliminarily Matched Hospitals
Since the AHA Annual Survey does not include information indicating that a
hospital has recently merged or been acquired (within the past three years) or was a party
to a future merger or acquisition (within three years into the future), the PSM and manual
matched list needed to be further examined, tested, and, if necessary, revised. For
example, if PSM or manual matching provided a matched hospital that merged or was
acquired in the past three years or within three years following the MOE or Acquisition
transaction, that hospital could not serve as an acceptable counterfactual hospital.
Each Matched hospital was examined to determine whether or not it was part of a
merger or acquisition (M&A) event during the applicable three years pre- or post-event.
The three years pre- or post-event period was determined by the transaction date of the
Event hospital being matched. For example, a matched hospital for an Event hospital that
closed a transaction in 2009 could not have completed a merger or acquisition transaction
three years pre- (2006-2008), in 2009, or three years post- (2010-2012) transaction. When
the examination identified a preliminarily matched hospital that was a party to its own
event during the applicable time period, an alternative match was sought using the
manual matching method.
The ILA reports served as the primary source for the examination and testing of
the Matched hospitals (to determine if a preliminarily matched hospital was a party to a
merger or acquisition in the applicable three-year time period prior to and following the
paired Event hospital’s transaction. For situations in which there was a question or
concern about the accuracy or confirmatory status in the ILA report, other sources were

used including Modern Healthcare, Becker’s Hospital Review, and a Google search. A
verifying note was entered into the database for each of the 172 Matched hospitals.
In some CBSAs (e.g., Chicago and Seattle), M&A activity was intense between
2006 to 2016. Consequently, otherwise suitable matches or alternative matches were
disqualified due to a recent or future M&A. This made it impossible to locate an
acceptable matched hospital for several Event hospitals.
Sixty-four of the preliminarily matched hospitals were disqualified for various
reasons including discovery of a time-overlapping merger or acquisition (52 occurrences),
PSM yielding a Veterans Administration hospital (inclusion/exclusion criteria specified
no government owned and operated hospitals) as a match (four occurrences), matched
hospital terminating operations within three years (six occurrences), and PSM yielding a
rural hospital more than 200 miles away from the Event hospital (two occurrences).
Twenty-five (25) of these hospitals were replaced with an alternative match using another
manual match process. The remaining 39 that could not be matched with the manual
matching process were eliminated, along with the corresponding Event hospital. This
resulted in 133 Event hospitals and 133 Matched hospitals (172 - 39 = 133).
Final Verification of the Event and Matched Hospitals
To ensure the highest level of accuracy, a final verification review was conducted
for all 266 Event and Matched hospitals. This review involved a hospital-by-hospital,
final quality assurance test of the inclusion and exclusion criteria along with a
confirmation of suitable matches. After all final examination and testing, 133 Event and
Matched hospital pairs remained.
Obtaining the HCAHPS Ratings – Elimination of 34 Pairs
HCAHPS data were provided by Press-Ganey (PG). PG is a publicly traded
company with over 3,000 hospital clients in the United States. PG’s primary service is

helping hospitals and health systems measure, manage, and optimize their patient
experience performance. PG is also one of the CMS-approved companies for providing
HCAHPS surveys and intermediating HCAHPS reporting to CMS.
Hospitals report their HCAHPS performance data to CMS on a quarterly basis
with a rolling, cumulative 12-month rating reported for each quarter. In other words, the
quarterly value reported by CMS reflects the hospital’s composite HCAHPS ratings for
the last 12 months.
The principal investigator sent PG a data file containing the name, address, NPI
number, and Medicare number for all 266 hospitals. PG imported the quarterly ratings for
each of the four HCAHPS domains. Thirty-four (34) Event hospitals along with their
counterfactual Matched hospitals were eliminated from the study due to missing
HCAHPS ratings for either one or both hospitals in the pair (68 hospitals removed in
total). In some cases, the Event and Matched hospital were critical access hospitals
(CAH). CAHs are not required to submit HCAHPS data to CMS. In other cases,
particularly for a merger or acquisition event that occurred in 2009, HCAHPS ratings
from 2007 (two years prior to the event) were not reported. In cases involving missing
HCAHPS ratings for a Matched hospital, additional efforts were made to find an
alternative matched hospital. No suitable matches were identified. Missing HCAHPS
ratings for an Event hospital resulted in the elimination of both the affected Event
hospital and the corresponding Matched hospital.
Complete HCAHPS ratings for the four HCAHPS domains (Overall,
PHYSICIAN, NURSE, and STAFF) and for all six time periods were available for 99
Event and 99 Matched hospitals (133 pairs – 34 pairs = 99 pairs). These 198 hospitals
defined the population of hospitals in this study. Appendix E contains the complete list of
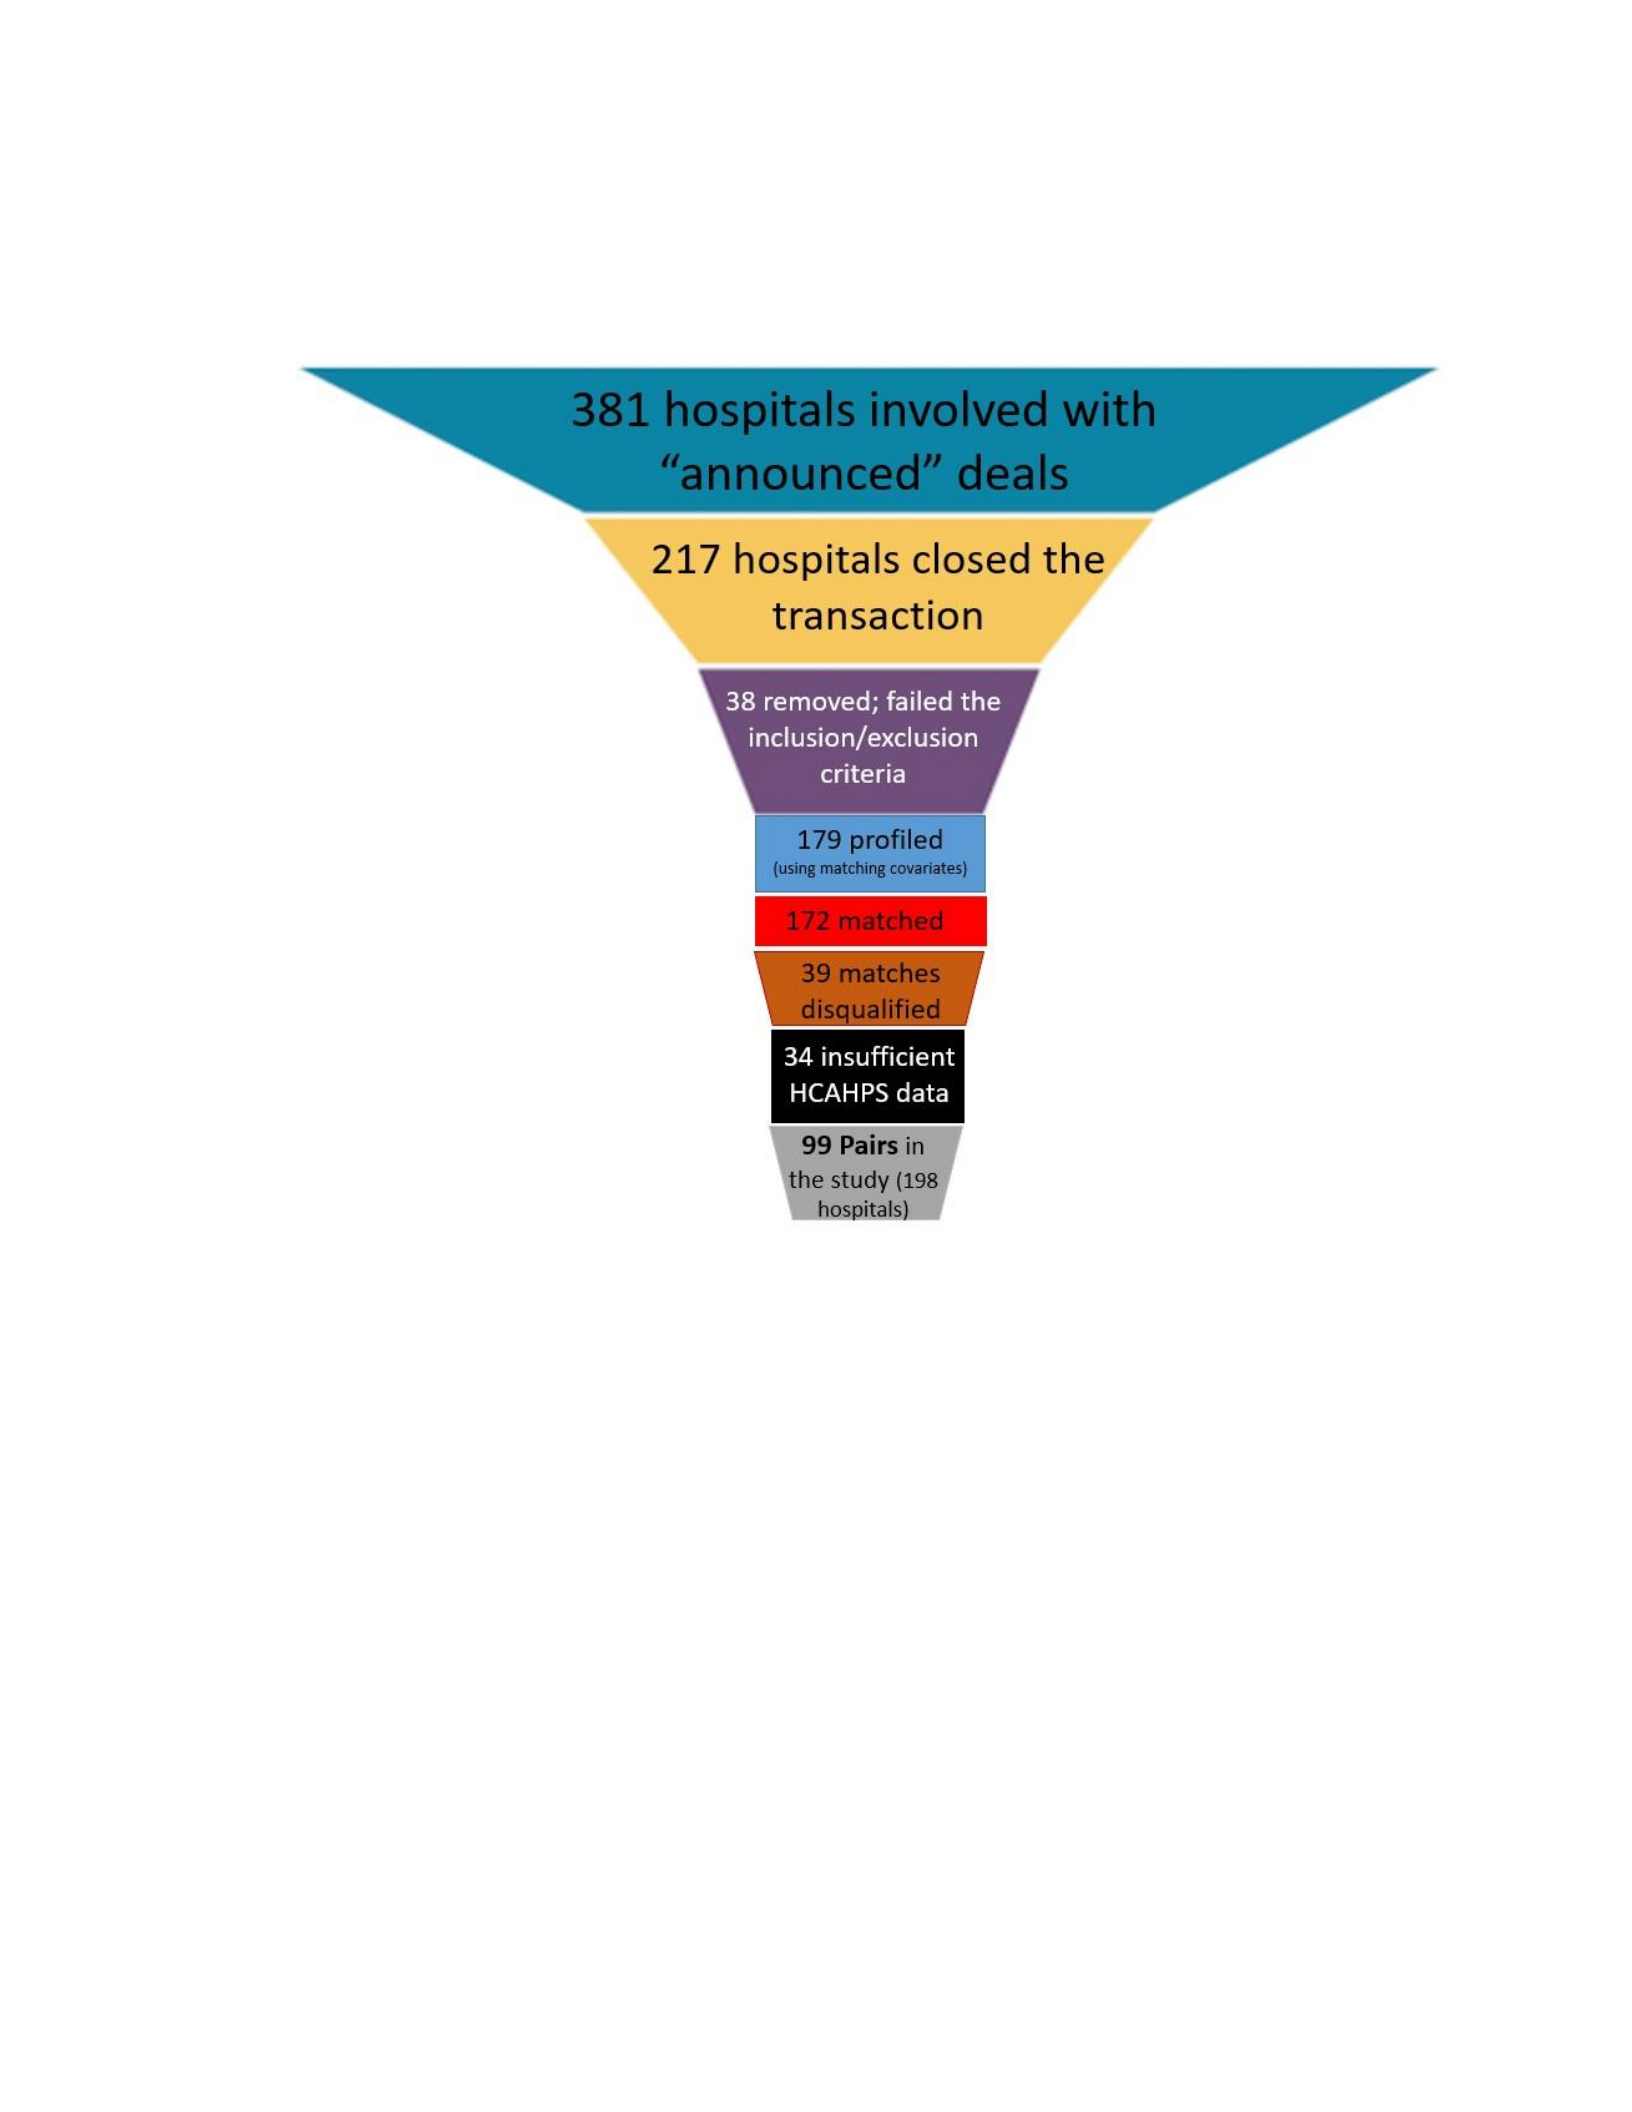
the final 198 hospitals included in the analytic sample. Figure 8 provides a graphical
summary of the identification and matching process.
Figure 8. Identification and matching process resulting in the 99 pairs.
Goodness-of-Match and Balance Diagnostics
One of the challenges in studies involving counterfactual subjects as a synthetic
control group is finding suitable matches (Campbell & Harper, 2012). Due to the number
of matching covariates involved, finding an “exact” match was not practical.
In the hierarchical matching algorithm for this study, geographic match was given
the highest priority. All 99 matched pairs in this study contain hospitals operating in the
same CBSA, an adjacent CBSA, or another rural area (non-CBSA) in the same state or
adjacent state within 200 miles of the Event hospital. The mean distance between the
Event and Matched hospital was 36.3 miles. There were only four sets of paired hospitals

located more than 100 miles apart, with all eight hospitals located in rural counties within
the same state or an adjacent state. Therefore, there was a moderate to high level of
geographic matching. As previously described, the rationale for prioritizing geographic
matching was to account for the demographic and cultural characteristics, economic
conditions, and secular factors that vary from one region of the United States to another.
Additionally, since hospitals in the same or a nearby region may compete for the same
market of patients, the HCAHPS performance of those in-region hospitals may exert
more competitive influence on each other versus a hospital from another region of the
United States. In other words, since patients tend to seek hospital care from hospitals near
their residence, the competitive actions and performance of hospitals near each other (i.e.,
in the same or adjacent CBSA or adjacent rural county) may be more influential on
decisions to improve access, quality, or patient service (Noether, 1987; Rivers & Glover,
2008; Zwanziger, Melnick, & Eyre, 1994).
The second most important matching criterion was size. All but four of the pairs
met the stipulated thresholds for size matching. A “size match” was deemed minimally
acceptable if the Event hospital matched on at least one of the three size-related variables
(licensed beds, admissions, and adjusted admissions). A “match” was defined as the
Event hospital being no less than 50% and no more than 200% the size of the Matched
hospital.
An exception to the “50%/200%” rule was made in four cases where size did not
match on at least one of the three size-related continuous variables (beds, admission, and
adjusted admissions). The first exception involved the match for the Elkhart General
Hospital-Indiana University Hospital Goshen (IUGH) pair. IUGH’s adjusted admissions
were within one-half of one percentage point from the 50% threshold. The second
exception involved the match for Memorial Hospital in York, Pennsylvania: York

Hospital. Although York Hospital is significantly larger, it is only seven miles away from
Memorial Hospital and is the only competing hospital in York, Pennsylvania. Both
hospitals matched for system status and profit status. The third exception involved the
match for Northern Michigan Hospital (NMH) in Petoskey, Michigan: Otsego Memorial
Hospital (OMH) in Gaylord, Michigan. OMH was only nine beds below the 50% cut-off
and both hospitals matched for system and profit status. In addition, OMH was the
nearest hospital to NMH with only 38 miles distance between the two and with both
hospitals serving overlapping geographic markets/regions. The final exception involved
the match for Nix Hospital in San Antonio, Texas: University Hospital in San Antonio.
Nix has 173 licensed beds or 16 short of the number needed to equal 50% of University
Hospital’s total licensed beds (378). University Hospital is only 11 miles away from Nix
and both draw their patients from an overlapping subsection of the San Antonio
metropolitan area.
To further test whether the Matched hospitals represented a reasonable
counterfactual comparison group, bivariate tests were conducted to assess whether there
were significant differences between the Event and Matched groups after matching (i.e.,
were the two groups balanced). Table 1 contains a summary of descriptive statistics
comparing the 99 Event hospitals to the 99 Matched hospitals. Paired t-testing was
performed using Stata 13 on the three size-related matching variables (continuous). There
was no significant difference between the Event and Matched hospitals with respect to
licensed beds (t=1.05, p=0.30) and admissions (t=1.55, p=0.13). There was a significant
difference with respect to adjusted admissions (t=9.44, p=0.001), with Matched hospitals
reporting more adjusted admissions (M=22,953; SD=19,177) than Event hospitals
(M=20,334; SD=14,634).
To test for balance between the 99 pairs of Event and Matched hospitals on the
two categorical variables (dummy variables) indicating profit status (for-profit or not-
forprofit) and system status (hospital was part of a system or a standalone independent
hospital), McNemar’s test were performed. The “mcc” command in Stata 13 was used.
Thirteen pairs had differences in profit status; however, the McNemar’s test found no
statistically significant difference between the two groups (McNemar’s Chi2=0.69,
p=0.41). Sixteen pairs had differences in system status. McNemar’s test found these
differences to be statistically significant (McNemar’s Chi2=4.0, p=0.046**).
Table 1
Summary of Information of the 99 Event Hospitals and 99 Matched Hospitals
Goodness of Fit Statistic
Event Matched
(Balance Test) (if Match?
Hospitals Hospitals
applicable)
Number of
99 99 1:1 ratio YES
hospitals
Event Year
2009 7
2010 14
2011 36
2012 20
2013 22
Merger Type
Merger of Equals
44 44 1:1 ratio YES
Hospitals
Acquired Hospitals 55 55 1:1 ratio YES
Number of Unique

CBSAs & Non- 65 65 YES
CBSA (rural areas)
Number of Unique
50 50 YES
CBSAs
Number of Unique
15 15 YES
Rural Areas
Number of U.S.
33 31
States
Same CBSA or 65 65 1:1 ratio
Rural Match
Mean Distance
Between the 99 Pairs 36.3 36.3
of Hospitals
Mean Distance for
76 Pairs in the Same 22.2 22.2
CBSA
Mean Distance for
the 23 Pairs in Rural 83.2 83.2
Areas
Licensed Beds
Mean t=1.05;
237 259 Paired t-test YES
p=0.30
Standard Deviation 190 236
Minimum 18 25
Maximum 1,037 1,516
Annual Admissions
Mean t=1.55;
10,962 11,962 Paired t-test YES

p=0.13
Standard Deviation 9,663 11,342
Minimum 307 137
Maximum 52,583 93,568
Event
Hospitals
Matched
Hospitals
Goodness of Fit
(Balance Test)
Statistic
(if
applicable)
Match?
Adjusted
Admissions
Mean
20,334
22,953
Paired t-test
t=9.44;
p=0.001**
NO
Standard Deviation
14,634
19,177
Minimum
618
137
Maximum
77,928
150,030
Tax Status
McNemar
Chi2=0.69
YES
For Profit
9
12
p=0.405
Not-for-Profit
90
87
System Status
McNemar
Chi24.0
NO
Part of a System
81
73
p=0.046**
Standalone (not part
of a system)
18
26
*100% of the Matching hospitals met the criteria for geographic matching.
HCAHPS Performance of the 99 Event and 99 Matched Hospitals
Appendix F contains 99 sets of graphs: one set for each matched pair of Event and
Matched hospitals. Each set contains four graphs: one for each of the four HCAHPS
ratings (OVERALL, PHYSICIAN Domain, NURSE Domain, and STAFF Domain).
Each of the four individual graphs reflects the year-ending ratings for each of the six
years (T1, T2, T3, T4, T5, and T6).
Final Balance Test: T-testing of the HCAHPS Ratings Prior to the M&A Event
To determine pre-event similarity in HCAHPS ratings (i.e., parallel trends assumption),
paired t-testing was conducted using Stata 13 for each HCAHPS domain for each of the
three pre-event time periods (T1, T2 and T3). The results, summarized in Table 2,
indicate no statistically significant difference in any of the pre-Event HCAHPS ratings
between the two groups of hospitals.

Collectively, based on these results, it can be concluded that up until the event
(the MOE or Acquisition), the 99 pairs of Event and Matched hospitals had similar
attributes in terms of geographic location, size, profit status, and HCAHPS performance.
Table 2
Goodness of Fit Testing of Pre-Event HCAHPS Ratings for T1, T2, and T3 Using Paired
T-Testing
Event
Hospitals
Matched
Hospitals
64.71%
Statistic
Match?
Mean Pre-Event HCAHPS
Ratings for T1
OVERALL
64.10%
t=0.71;
p=0.48
YES
PHYSICIAN Domain
78.92%
78.72%
t=0.40;
p=0.69
YES
NURSE Domain
73.38%
73.91%
t=0.23;
p=0.82
YES
STAFF Domain
59.66%
60.70%
t=1.34;
p=0.18
YES
Mean Pre-Event HCAHPS
Ratings for T2
OVERALL
65.47%
65.97%
t=0.59;
p=0.55
YES
PHYSICIAN Domain
78.89%
78.81%
t=0.15;
p=0.88
YES
NURSE Domain
74.75%
75.09%
t=0.68;
p=0.50
YES
STAFF Domain
60.98%
62.00%
t=1.49;
p=0.14
YES
Mean Pre-Event HCAHPS
Ratings for T3
OVERALL
66.81%
67.20%
t=0.46;
p=0.64
YES
PHYSICIAN Domain
78.89%
78.97%
t=0.18;
p=0.86
YES
NURSE Domain
76.04%
76.01%
t=0.06;
p=0.95
YES
STAFF Domain
62.41%
62.90%
t=0.60;
p=0.55
YES
Paired T-Testing of HCAHPS Means Post-Event
Paired t-tests were conducted to provide additional descriptive statistics of the

HCAHPS performance of the Event and Matched hospitals for each of the three years
(T4, T5 and T6) post-event (Table 3). Since a paired t-test is limited to a “snapshot
comparison” of one year’s HCAHPS ratings, this study did not rely upon the results of
individual year paired t-testing to evaluate any of the 12 hypotheses. This study’s aim was
to determine the effect of a merger or acquisition event on HCAHPS performance
“over time” or from “year to year” (i.e., the temporal effects on the rate of change).
Although useful for descriptive purposes, paired t-testing of individual years could not
fully evaluate study’s hypotheses.
Analytic Strategy for Testing Study Hypotheses
One statistical test, fixed effects difference-in-differences (FEDID), was used to
test the 12 hypotheses and answer the temporal differences questions (i.e., the rate of
changes in HCAHPS ratings over time).
FEDID Tests
Cross-sectional FEDID testing was utilized to answer the question of whether
HCAHPS performance of the two groups (Event hospitals and Matched hospitals)
changes differently over time. FEDID is a multivariate modeling approach that is
designed to minimize the potential impact of omitted variable bias, especially (relatively)
stable yet unobserved factors (e.g., organizational culture, management style) that may
differ between two groups of subjects in this study (Event versus Matched hospitals), and
bias the study results (Qui, Kirkeide, & Wang, 2018). By including fixed effects (hospital
dummies), one can account and control for these differences between subjects. The fixed
effects effectively “soak up all the across-group action” leaving only the “within-group
action” (Blumenstock, 2016, p. 7). Time period dummy variables account for temporal
changes in HCAHPS scores.

The 12-month time period immediately preceding the merger/event year (T3) was
chosen as the referent time period for comparison purposes because that year reflects the
HCAHPS ratings for the last 12-month period the Event hospital operated outside the
influence of a merger or acquisition. In other words, T3 reflects HCAHPS performance
prior to the potentially disruptive effects of a merger or acquisition. In addition, with the
exception of a minor difference in the PHYSICIAN domain ratings (0.03 lower in T3 vs.
T1), the HCAHPS ratings of the Event hospitals were at their highest level in T3
compared to T1 or T2. Selecting T1 or T2 as the pre-event referent year could have biased
the results of FEDID testing since a year with lower values would have served as the
baseline.
The FEDID model is specified below:
HCAHPSit= + 1Eventi + 2T4 + 3T5 + 4T6 + 5Eventi*T4 + 6Eventi*T5 +
7Eventi*T6 + εit
Where “i” indexes hospitals; HCAHPS is the hospital’s patient experience rating; Event is
the indicator for whether a hospital merged or not; and “T” indicates the post-merger,
year-ending time period (T4, T5, and T6).
MOE vs. Acquired Hospitals
Given the study’s interest in testing whether a merger event was more disruptive
among MOE hospitals compared to Acquisition hospitals (i.e., H3a-H3d), an additional
set of FEDID models were estimated that included two new dummy variables that
distinguished between the two types of events: MOE (merger-of-equal) hospitals and
Acquired hospitals. T3 was the referent time period and Acquired hospitals served as the
referent group. This FEDID model is specified as:
HCAHPSit= + 1MOEi + 2Acquisitiont + 3MOEi*T4 + 4Acquisitioni*T4 +
5MOEi*T5 + 6Acquisitioni*T5 + 7MOEi*T6 + 8Acquisitioni*T6 + εit

Where “i” indexes hospitals; HCAHPS is the hospital’s patient experience score; MOE is
the indicator for whether a hospital experienced a Merger-of-Equals; Acquisition is the
indicator for whether a hospital experienced an acquisition; and “T” indicates the
postmerger, year-ending time period (T4, T5, and T6).
Levels of Statistical Significance – P-value Thresholds
Due to the relatively modest sample size, two levels of statistical significance
were considered in the study:
• p < 0.05, which was designated with two asterisks (**)
• p < 0.10, which was designated with one asterisk (*).
CHAPTER 4
RESULTS
Chapter 4 summarizes the results of statistical testing conducted to provide
descriptive information and evaluate the 12 hypotheses. The results are organized and
presented in six sections:
• Section One: Paired T-Testing of Individual Year HCAHPS Mean Ratings
(T1-T6)
• Section Two: FEDID Testing of OVERALL Ratings
• Section Three: FEDID Testing of PHYSICIAN Domain Composite Ratings
• Section Four: FEDID Testing of NURSE Domain Composite Ratings
• Section Five: FEDID Testing of STAFF Composite Domain Ratings, and
• Section Six: FEDID Testing to Evaluate HCAHPS Ratings by Merger Event
Type (44 Merger-of-Equals hospitals and 55 Acquired hospitals).

Section One: Paired T-Testing of Individual Year HCAHPS Mean Ratings (T1-T6)
Tables 2 and 3 provide a descriptive summary of the paired t-tests of the six individual
years and the four HCAHPS ratings. Table 2 contains the pre-event information (T1, T2,
and T3) and Table 3 contains the post-event information (T4, T5, and T6). As mentioned
previously, paired t-testing found no statistical difference between the Event hospitals and
Matched hospitals in any of the three pre-event years (T1, T2 and T3). For all three pre-
event years and for all four HCAHPS ratings, there was approximately 1% or less
difference between the two groups. The lowest p-value in Table
2 (p=0.14) was in T2 for the STAFF domain.
The post-event results summarized in Table 3 reflect six significant “within year”
differences between the two groups. The OVERALL, NURSE domain, and STAFF
domain ratings for T5 and T6 were significantly different between Event hospitals and
Matched hospitals. There were no statistically significant differences in the PHYSICIAN
domain ratings in any of the three post-event years. Likewise, there were no differences
in the OVERALL, NURSE domain, and STAFF domain ratings for T4.
Consistent with the study’s method described in Chapter 3, paired t-testing (for
both the pre-event and post-event years) was used for descriptive purposes only.

Table 3
Post-Event HCAHPS Ratings Comparisons for T4, T5, and T6 Using Paired T-Testing
Event
Hospitals
Matched
Hospitals
Statistic
Mean Post-Event HCAHPS
Ratings for T4
OVERALL
67.76%
68.74%
t=1.22;
p=0.23
PHYSICIAN Domain
79.63%
79.29%
t=0.80;
p=0.42
NURSE Domain
76.59%
77.03%
t=0.97;
p=0.33
STAFF Domain
63.70%
64.42%
t=1.05;
p=0.30
Mean Post-Event HCAHPS
Ratings for T5
OVERALL
68.11%
69.80%
t=2.14;
p=0.03**
PHYSICIAN Domain
79.84%
79.82%
t=0.05;
p=0.96
NURSE Domain
77.12%
78.17%
t=2.32;
p=0.02**
STAFF Domain
63.56%
64.97%
t=2.10;
p=0.04**
Mean Post-Event HCAHPS
Ratings for T6
OVERALL
68.56%
70.03%
t=1.84;
p=0.07*
PHYSICIAN Domain
79.80%
79.89%
t=0.19;
p=0.85
NURSE Domain
77.73%
78.72%
t=2.38;
p=0.02**
STAFF Domain
64.35%
65.79%
t=2.39;
p=0.02**
The following sections – organized by HCAHPS domain - provides more details on these
comparisons.
OVERALL Rating
For T4, the OVERALL mean ratings for both groups increased, with the
percentage of patients rating their patient experience as a “9” or “10” (i.e., average top
box score) increasing from 66.81% in T3 to 67.76% in T4 for the 99 Event hospitals, an
increase of 0.95 percentage points. Likewise, mean ratings for the Matched hospitals

increased from 67.20% in T3 to 68.74% in T4. The paired t-test, however, indicated that
the difference between the two groups in average overall experience ratings was not
statistically significant in the time period immediately following the merger (t(98)=1.22,
p=0.23).
For T5, both groups again experienced an increase in OVERALL patient
experience, with a mean rating of 68.11% for the EHs (an increase of 0.35 percentage
points above T4), and mean score of 69.80% for the MHs (an increase of 1.06 percentage
points above T4). A paired t-test found a significant difference between the two groups of
hospitals (t(98)=2.14, p= 0.035), with the EHs reporting lower ratings (M=68.11%,
SD=0.075) than MHs (M=69.80%, SD=0.064).
Both groups continued the trend of increasing OVERALL patient experience
ratings in T6, with a mean ratingof 68.56% for the EHs (an increase of 0.45 above T5),
and mean rating of 70.03% for the MHs (an increase of 0.23 above T5). A paired t-test
found that the difference in ratings between these two groups of hospitals was statistically
significant in the T6 period (t(98)=1.84, p= 0.069), with EHs reporting lower scores
(M=68.56%, SD=0.070) than MHs (M=70.03%, SD=0.064).
PHYSICIAN Domain Composite Rating
For T4, the mean top box ratings (the percentage of patients giving an “always”
rating) for both groups increased with EH mean ratings increasing from 78.89% in T3 to
79.63% in T4. The MHs experienced an absolute percentage point increase of 0.32, from
78.97% in T3 to 79.29% in T4. A paired t-test found no significant difference in the T4
PHYSICIAN domain composite ratings (t(98)=-0.80, p=0.42), with the EHs reporting
higher scores (M=79.63, SD=0.037) than the MHs (M=79.29, SD=0.036).
For T5, both groups experienced an increase in PHYSICIAN domain ratings with
a mean score of 79.84 for the EHs (an increase of 0.20 above T4), and mean score of

79.82 for the MHs (an increase of 0.53 above T4). The paired t-test, however, indicated
no significant difference (t(98)=-0.05, p= 0.96) with the EHs (M=79.84, SD=0.037) and
MHs (M=79.84, SD=0.037) having nearly identical scores in the T5 period.
For T6, both groups experienced an increase in PHYSICIAN domain ratings with
a mean score of 79.80 for the EHs while the mean rating for the MHs increased by 0.07 to
79.89. A paired t-test found no significant difference in the T6 PHYSICIAN rating
(t(98)=0.19, p= 0.85), with the EHs, again, reporting nearly identical scores (M=79.80,
SD=0.035) as the MHs (M=79.89, SD=0.037).
NURSE Domain Composite Rating
For T4, the mean top box ratings (the percentage of patients giving an “always”
rating) for both groups increased with the EH mean ratings increasing from 76.04 in T3 to
76.59 in T4. The MHs experienced an absolute increase of 1.02 in T4, from 76.01 in T3
to 77.03 in T4. A paired t-test indicated no significant difference in the T4 NURSE ratings
(t(98)=0.19, p= 0.85), with the EHs (M=76.59, SD=0.042) reporting lower scores than the
MHs (M=77.03, SD=0.040).
For T5, both groups experienced an increase in NURSE ratings with a mean score
of 77.12 for the EHs (an increase of 1.08 above T4), and mean score of 78.17 for the
MHs (an increase of 1.14 above T4). The paired t-test found a significant difference in the
T5 NURSE ratings (t(98)=2.32, p= 0.022), with the EHs reporting lower ratings
(M=77.12%, SD=0.041) than the MHs (M=78.12%, SD=0.041).
For T6, both groups experienced an increase in NURSE ratings with a mean rating
of 77.73% for the EHs (an increase of 0.61 above T5), and a mean rating of 78.72% for
the MHs (an increase of 0.55 above T5). A paired t-test found a significant difference in
the T6 NURSE ratings (t(98)=2.38, p= 0.02), with the EHs reporting lower ratings
(M=77.73%, SD=0.038) than MHs (M=78.72%, SD=0.038).

STAFF Domain Composite Rating
For T4, the mean top box ratings (the percentage of patients giving an “always”
rating) for both groups increased with the EH mean ratings increasing from 62.41% in T3
to 63.70% in T4. The MHs experienced an absolute increase of 1.52 percentage points in
T4. However, a paired t-test found no significant difference between the two hospital
groups for the T4 period (t(98)=1.05, p=0.30), with the EHs reporting lower ratings
(M=63.70%, SD=0.069) than MHs (M=64.42%, SD=0.067).
For T5, the EHs’ mean STAFF rating was 63.56% (a decrease of 0.14 compared to
T4). The MHs had a mean rating of 64.97% (an increase of 0.55 above T5). The paired t-
test found a significant difference in the T5 STAFF rating (t(98)=2.10, p=0.04), with the
EHs reporting lower ratings (M=63.56%, SD=0.066) than the MHs (M=64.97%,
SD=0.066).
For T6, both groups experienced an increase in STAFF HCAHPS ratings with a
mean rating of 64.35% for the EHs (an increase of 0.79 above the prior year), and mean
rating of 65.79% for the MHs (an increase of 0.82 above the prior year). A paired t-test
found a significant difference in the T6 STAFF ratings (t(98)=2.39, p=0.02), with the EHs
reporting lower scores (M=64.35%, SD=0.063) than the MHs (M=65.79%,
SD=0.063).
Section Two: FEDID Testing of the OVERALL Rating
This section summarizes the results of FEDID testing performed to evaluate
Hypothesis 1 and 4a. Table 4 contains a summary of the FEDID tests of the OVERALL
rating for the three post-event years (T4, T5, and T6) with T3 serving as the referent year.
Table 4
Post-Event OVERALL Rating
Variable
Mean Rating (%)
Beta (SE)
P-Value

T3 Event Hospitals
66.81
T4 Event Hospitals
67.76
T5 Event Hospitals
68.11
T6 Event Hospitals
68.56
T3 Matched Hospital
67.20
T4 Matched Hospital
68.74
T5 Matched Hospital
69.80
T6 Matched Hospital
70.03
Interaction Terms
Event*T4
-0.006 (0.006)
0.34
Event*T5
-0.013 (0.007)
0.07*
Event*T6
0.011 (0.008)
0.17
Non-Interaction Terms
Event Hospitals
-0.004 (0.010)
0.70
1st Post-Event (T4)
0.015 (0.004)
0.00**
2nd Post-Event (T5)
0.026 (0.004)
0.00**
3rd Post-Event (T6)
0.028 (0.005)
0.00**
Referent Group: Matched hospitals
Referent Year: T3 (12-month period prior to Event)
Controlling for relatively stable, hospital-level characteristics, the increase in
OVERALL ratings from T3 to T4 was smaller for EHs, on average, compared to their
matched counterparts, although the difference was not statistically significant (b= -0.006,
p=0.34). The increase in OVERALL ratings from T3 to T5 for Event hospitals was again
smaller, on average, compared to Matched hospitals, and in this case the difference was
statistically significant (b= -0.013, p=.07). The results for the three-year post-merger time
period (T6) were similar to those for the time period immediately following merger (T4).
Specifically, the increase in Overall HCAHP ratings from T3 to T6 was smaller for Event
hospitals, on average, compared to Matched hospitals, although the difference was, once
again, not statistically significant (b= -0.011, p=0.17).

In sum, the results of the analysis supported Hypothesis 1: a hospital’s overall
patient experience ratings will be negatively affected by having recently completed a
merger (within the last 12-24 months). The overall patient experience ratings of recently
merged hospitals will be lower compared to the overall patient experience ratings of
similar hospitals that did not merge. The negative relationship between a merger and a
hospital’s OVERALL ratings occurred in T5, the second year (months 13-24) following
the merger event.
The results also supported Hypothesis 4a: Event hospitals’ overall patient
experience ratings will return to normal levels within 36 months post-merger with no
performance difference compared to similar hospitals that did not merge. For T6 (three
years post-event), there was no difference in OVERALL ratings between the Event
hospitals and Matched hospitals. The statistically significant, negative relationship found
in T5 did not continue in T6.
Section Three: FEDID Testing of the PHYSICIAN Domain Composite Ratings
This section summarizes the results of FEDID testing performed to evaluate hypotheses
H2a and H4b. Table 5 contains a summary of the PHYSICIAN domain HCAHPS ratings
and FEDID tests for each post-merger year (T4, T5, and T6) with T3 serving as the
referent year.
Table 5
Post-Event PHYSICIAN Domain Composite Ratings
Variable T3
Event Hospitals
Mean Rating (%)
78.89
Beta (SE)
P-Value
T4 Event Hospitals
79.63
T5 Event Hospitals
79.64
T6 Event Hospitals
79.80
T3 Matched Hospital
78.97
T4 Matched Hospital
79.29
T5 Matched Hospital
79.82
T6 Matched Hospital
79.89
Interaction Terms
Event*T4
0.004 (0.004)
0.27
Event*T5
0.001 (0.004)
0.82
Event*T6
0.001 (0.004)
0.80
Non-Interaction Terms
Event Hospitals
-0.001 (0.005)
0.88
1st Post-Event (T4)
0.003 (0.003)
0.22
2nd Post-Event (T5)
0.008 (0.003)
0.001**
3rd Post-Event (T6)
0.009 (0.003)
0.001**
Referent Group: Matched hospitals
Referent Year: T3 (12-month period prior to Event)
The mean PHYSICIAN domain HCAHPS ratings of the EHs increased 0.74 from
T3 (12 months prior to the merger) to T4 (first year post-merger). During this same time
interval, the Matched hospitals’ mean PHYSICIAN domain ratings increased by 0.32.
Although the increase for EHs was greater than for MHs, the difference was not
significant (b= 0.004, p=0.27).
The mean PHYSICIAN domain ratings of the EHs increased 0.95 from T3 (12
months prior to the merger) to T5 (second year post-merger). During this same time
interval, the MHs’ mean PHYSICIAN domain ratings increased by 0.85. The change in
ratings between T5 and T3, however, was not significantly different for EHs and MHs
(b= 0.001, p=0.816).
The mean PHYSICIAN domain ratings of the EHs increased 0.91 from T3 (12
months prior to the merger) to T6 (third year post-merger). During this same time

interval, the Matched hospitals’ mean PHYSICIAN domain ratings increased by 0.91.
Once again, the change between T6 and T3 did not differ significantly for EHs and MHs
(b= 0.001, p=0.802).
In sum, the analysis did not support Hypothesis 2a: a hospital’s physician
communications ratings will be negatively affected by having recently completed a
merger (within the last 12-24 months). Patient ratings of physician communications for
recently merged hospitals will be lower compared to the ratings of physician
communications for similar hospitals that did not merge. There was no post-merger effect
on PHYSICIAN domain ratings.
There was support for Hypothesis 4b: there will be no difference in physician
communications ratings between merged and similar unmerged hospitals three years
following the merger. However, the finding of “no difference” in T6 was not due to a
rebound in the PHYSICIAN Domain ratings for the EHs from T4 and T5. PHYSICIAN
Domain ratings between the EHs and MHs remained statistically similar for all six years
tested using both paired t-tests and FEDID testing.
Section Four: FEDID Testing of the NURSE Domain Composite Ratings
This section summarizes the results of the statistical testing performed to evaluate
hypotheses H2b and H4c. Table 6 contains a summary of the NURSE domain HCAHPS
ratings and FEDID results each of the three post-merger years (T4, T5, and T6).
Table 6
Post-Event NURSE Domain Composite Ratings
Variable
Mean Rating (%)
Beta (SE)
P-Value
T3 Event Hospitals
76.04
T4 Event Hospitals
76.59
T5 Event Hospitals
77.12
T6 Event Hospitals
77.73

T3 Matched Hospital
76.01
T4 Matched Hospital
77.03
T5 Matched Hospital
78.17
T6 Matched Hospital
78.82
Interaction Terms
Event*T4
-0.005 (0.004)
0.24
Event*T5
-0.108 (0.005)
0.02**
Event*T6
-0.010 (0.005)
0.055*
Non-Interaction Terms
Event Hospitals
0.003 (0.006)
0.96
1st Post-Event (T4)
0.010 (0.003)
0.00**
2nd Post-Event (T5)
0.023 (0.003)
0.00**
3rd Post-Event (T6)
0.027 (0.003)
0.00**
Referent Group: Matched hospitals
Referent Year: T3 (12-month period prior to Event)
The mean, NURSE domain top box ratings of the EHs increased 0.55 from T3 (12
months prior to the merger) to T4 (first year post-merger). During this same time interval,
the Matched hospitals’ mean NURSE domain top box ratings increased by 1.02.
Although the increase for EHs was smaller than for Matched hospitals, after controlling
for other factors, the change in NURSE domain ratings between T3 and T4 for EHs was
not significantly different than MHs (b=-0.005, p=0.24).
The mean, NURSE domain ratings of the EHs increased 1.08 percentage points
from T3 (12 months prior to the merger) to T5 (second year post-merger). During this
same time interval, the Matched hospitals’ mean NURSE domain ratings increased by
2.16. The change in NURSE domain scores between T5 and T3 was significantly smaller
for EHs compared to MHs (b=-0.108, p=0.02).
The mean NURSE domain ratings of the EHs increased 1.69 percentage points
from T3 (12 months prior to the merger) to T6 (third year post-merger). During this same
time interval, the Matched hospitals’ mean NURSE domain ratings increased by 2.71

percentage points. Similar to T5, the increase in NURSE domain ratings fromT6 to T3
was significantly smaller for EHs compared to MHs (b=-0.010, p=0.06).
In sum, the results of the analysis supported Hypothesis 2b: a hospital’s nurse
communications ratings will be negatively affected by having recently completed a
merger (within the last 12-24 months). Patient ratings of nurse communications for
recently merged hospitals will be lower compared to the ratings of nurse communications
for similar hospitals that did not merge. The NURSE domain ratings of the EHs in T5
(second year following the merger) were significantly lower compared to the MHs, which
was consistent with H2b.
However, the results did not support Hypothesis 4c: there will be no difference in
nurse communications ratings between merged and similar unmerged hospitals three
years following the merger. FEDID tests found a statistically significant difference in the
Nurse Domain ratings between EHs and MHs for T6 (three years post-event), indicating
the NURSE domain performance did not rebound in T6.
Section Five: FEDID Testing of the STAFF Domain Composite Ratings
This section provides the results of the statistical testing performed to evaluate
hypotheses H2c and H4d. Table 7 contains a summary of the results from the FEDID
testing on the STAFF domain rating each post-event year (T4, T5, and T6).
Table 7
Post-Event STAFF Domain Composite Ratings
Variable
Mean Rating (%)
Beta (SE)
P-Value
T3 Event Hospitals
62.41
T4 Event Hospitals
63.70
T5 Event Hospitals
63.56
T6 Event Hospitals
64.35
T3 Matched Hospital
62.90

T4 Matched Hospital
64.42
T5 Matched Hospital
64.97
T6 Matched Hospital
65.79
Interaction Terms
Event*T4
-0.002 (0.006)
0.69
Event*T5
-0.009 (0.007)
0.21
Event*T6
-0.009 (0.008)
0.22
Non-Interaction Terms
Event Hospitals
0.005 (0.010)
0.61
1st Post-Event (T4)
0.015 (0.004)
0.00**
2nd Post-Event (T5)
0.021 (0.004)
0.00**
3rd Post-Event (T6)
0.029 (0.004)
0.00**
Referent Group: Matched hospitals
Referent Year: T3 (12-month period prior to Event)
The mean STAFF domain ratings of the EHs increased 1.29 percentage points
from T3 (12 months prior to the merger) to T4 (first year post-merger). During this same
time interval, the Matched hospitals’ mean STAFF domain ratings increased by 1.52
percentage points. Although the increase for EHs was smaller compared to Matched
hospitals, the difference was not statistically significant (b= -0.002, p=0.69).
The mean STAFF domain ratings of the EHs increased 1.15 percentage points
from T3 (12 months prior to the merger) to T5 (second year post-merger). During this
same time interval, the MHs’ mean STAFF domain ratings increased by 2.07 percentage
points. The change in STAFF ratings from T5 to T3 was not significantly different
between EHs and MHs (b= -0.009, p=0.21).
The mean STAFF domain ratings of the EHs increased 1.94 percentage points
from T3 (12 months prior to the merger) to T6 (third year post-merger). During this same
time interval, the MHs’ mean STAFF domain ratings increased by 2.89 percentage points.
Once again, the difference between EHs and MHs was not statistically significant (b= -
0.0009, p=0.22).

In sum, the results of the analysis did not support Hypothesis 2c: a hospital’s staff
responsiveness ratings will be negatively affected by having recently completed a merger
(within the last 12-24 months). Patient ratings of staff responsiveness for recently merged
hospitals will be lower compared to the ratings of nurse communications for similar
hospitals that did not merge.
The results did support Hypothesis 4d: There will be no difference in staff
responsiveness ratings between merged and similar unmerged hospitals three years
following the merger. However, the finding of “no difference” in T6 was not the result of
performance improvement following a period of post-merger performance decline.
Rather, the analysis found no difference between EHs and MHs in STAFF domain ratings
for any of the three post-merger years.
Section Six: FEDID Testing of the HCAHPS Ratings of the 44 MOE Hospitals
Compared to the 55 Acquired Hospitals
This final section of Chapter 4 summarizes the results of the analysis used to
evaluate hypotheses H3a (OVERALL rating), H3b (PHYSICIAN Domain), H3c
(NURSE Domain), and H3d (STAFF Domain). These four hypotheses were based upon
supporting theories and empirical research that suggests greater post-merger disruption
and performance decline among organizations coming together via an MOE versus an
Acquisition (Devine, Lamont, & Harris, 2016; Lodorfos & Boateng, 2006). Applied to
this study on hospital mergers, these four hypotheses posited a negative relationship
between MOE hospitals and HCAHPS ratings compared to Acquired hospitals and
HCAHPS ratings.
Table 8 provides a summary of the four categories of HCAHPS ratings, by year,
for each of the two subgroups of Event hospitals (55 MOE hospitals and 44 Acquired
hospitals). Tables 9 through 12 summarize the FEDID testing, specifically the beta
coefficients, for each of the three post-event years and for each of the four categories of
(
%
)
%
)
(
(
)
%
79.00
73.80
58.55
HCAHPS ratings (OVERALL, PHYSICIAN Domain, NURSE Domain, and STAFF
Domain).
Table 8
HCAHPS Ratings by Merger Type
OVERALL PHYSICIAN NURSE Domain STAFF Domain
Domain
Acquire MOE Acquired MOE Acquire MOE Acquired MOE d (%) (%) (%) d (%) (%)
T1 63.29 65.11 78.85 73.76 60.55
T2
64.13
67.16
79.11
78.75
79.11
78.75
60.95
61.02
T3
65.78
68.09
79.29
78.39
79.29
78.39
63.38
61.20
T4
66.58
69.23
79.51
79.77
79.51
79.77
64.00
63.32
T5
66.36
70.30
79.71
80.00
79.71
80.00
63.38
63.77
T6
66.78
70.77
79.64
80.00
79.64
80.00
64.55
64.11
Table 9
FEDID Testing: Post-Event OVERALL Rating by Merger Type
Variable
Beta (SE)
P-Value
Interaction Terms
MOE*T4
0.003 (0.009)
0.72
MOE*T5
0.016 (0.011)
0.14
MOE*T6
0.017 (0.012)
0.15
Non-Interaction Terms
MOE Hospitals
0.023 (0.015)
0.12
1st Post-Event (T4)
0.008 (0.007)
0.27
2nd Post-Event (T5)
0.005 (0.008)
0.48
3rd Post-Event (T6)
0.010 (0.009)
0.28
Referent Group: Acquired hospitals
Referent Year: T3 (12-month period prior to Event)
Table 10
FEDID Testing: Post-Event PHYSICIAN Domain Composite Ratings by Merger Type
Variable
Beta (SE)
P-Value
Interaction Terms
MOE*T4
0.012 (0.005)
0.03**
MOE*T5
0.012 (0.007)
0.09*
MOE*T6
0.011 (0.007)
0.13

Non-Interaction Terms
MOE Hospitals
-0.009 (0.008)
0.26
1st Post-Event (T4)
0.002 (0.003)
0.52
2nd Post-Event (T5)
0.004 (0.005)
0.38
3rd Post-Event (T6)
0.005 (0.005)
0.24
Referent Group: Acquired hospitals
Referent Year: T3 (12-month period prior to Event)
Table 11
FEDID Testing: Post-Event NURSE Domain Composite Ratings by Merger Type
Variable
Beta (SE)
P-Value
Interaction Terms
MOE*T4
0.012 (0.006)
0.03**
MOE*T5
0.016 (0.007)
0.03**
MOE*T6
0.018 (0.008)
0.03**
Non-Interaction Terms
MOE Hospitals
-0.005 (0.008)
0.51
1st Post-Event (T4)
-1.35 (0.004)
1.00
2nd Post-Event (T5)
0.003 (0.006)
0.52
3rd Post-Event (T6)
0.009 (0.007)
0.16
Referent Group: Acquired hospitals
Referent Year: T3 (12-month period prior to Event)
Table 12
FEDID Testing: Post-Event STAFF Domain Composite Ratings by Merger Type
Variable
Beta (SE)
P-Value
Interaction Terms
MOE*T4
0.015 (0.009)
0.098*
MOE*T5
0.016 (0.007)
0.03**
MOE*T6
0.018 (0.008)
0.03**
Non-Interaction Terms
MOE Hospitals
-0.005 (0.008)
0.51
1st Post-Event (T4)
-1.35 (0.004)
1.00
2nd Post-Event (T5)
0.003 (0.006)
0.52
3rd Post-Event (T6)
0.009 (0.007)
0.16
Referent Group: Acquired hospitals
Referent Year: T3 (12-month period prior to Event)
FEDID Testing of the OVERALL Ratings for the Three Post-Merger Years (T4, T5 &
T6)
The mean OVERALL rating of the 44 MOE hospitals increased 1.14 percentage
points from T3 (12 months prior to the merger) to T4 (first year post-merger). During this

same time interval, the mean OVERALL rating of Acquired hospitals increased by 0.80
percentage points. MOE hospitals increased by 2.20 percentage points in T5 compared to
T3, and by 2.68 percentage points in T6 compared to T3. In comparison, the Acquired
hospitals’ OVERALL ratings increased by 0.58 percentage points in T5 compared to T3,
and by 1.00 percentage points in T6 compared to T3.
Although the comparative increases in the OVERALL ratings for MOE hospitals
were larger than for Acquired hospitals, FEDID testing found that the changes for MOE
hospitals were not significantly different than the Acquired hospitals for T4, T5 and T6
compared to T3 (respectively, b= 0.003, p=0.719; b=0.016, p=0.14; b=0.017, p=0.15).
In sum, although the MOE hospitals’ year-over-year increases were greater than
the corresponding increases among the Acquired hospitals, the differences were not
significantly different. Thus, there was no support for H3a.
FEDID Testing of the PHYSICIAN Domain Composite Ratings for the Three
PostMerger Years (T4, T5 & T6)
The mean PHYSICIAN domain rating of the 44 MOE hospitals increased 1.39
percentage points from T3 (12 months prior to the merger) to T4 (first year post-merger).
During this same time interval, the mean PHYSICIAN rating of Acquired hospitals
increased by 0.22 percentage points. MOE hospitals increased by 1.61 percentage points
in T5 compared to T3, and by 1.61 in T6 compared to T3. The Acquired hospitals, on
average, increased by 0.42 percentage points in T5 compared to T3, and by 0.35 in T6
compared to T3.
FEDID testing found the positive changes in PHYSICIAN ratings between T3 and
T4 and T5 to be significantly greater for MOE hospitals compared to Acquired hospitals
(respectively, b= 0.012, p=0.03; b=0.012, p=0.09). The positive changes in PHYSICIAN
ratings between T3 and T6, however, were not significantly different between MOE
hospitals and Acquired hospitals (b=0.011, p=0.13).

Collectively, this pattern of results is the opposite relationship than what H3b
posited, thus, the findings support the opposite relationship with MOE hospitals
performing better than Acquired hospitals; therefore, H3b was not supported.
FEDID Testing of the NURSE Domain Composite Ratings for the Three PostMerger
Years (T4, T5 & T6)
The mean NURSE ratings of the 44 MOE hospitals increased 1.23 percentage
points from T3 (12 months prior to the merger) to T4 (first year post-merger). During this
same time interval, the mean NURSE ratings of Acquired hospitals stayed the same (no
increase or decrease). MOE hospitals increased by 1.98 percentage points in T5 compared
to T3, and by 2.66 percentage points in T6 compared to T3. The Acquired hospitals
increased by 0.36 percentage points in T5 compared to T3, and by 0.91 in T6 compared to
T3. FEDID testing found the changes in NURSE rating for all three postmerger years
were significantly different, on average, between MOE hospitals and Acquired hospitals
(T4, T5, and T6, respectively: b= 0.012, p=0.03; b=0.02, p=0.03; b=0.018, p=0.03).
In sum, instead of Acquired hospitals performing comparatively better
postmerger, MOE hospitals’ performance was significantly better than the Acquired
hospitals. Thus, the findings did not support H3c.
FEDID Testing of the STAFF Domain Composite Ratings for the Three PostMerger
Years (T4, T5 & T6)
The mean STAFF ratings of the 44 MOE hospitals increased 2.11 percentage
points from T3 (12 months prior to the merger) to T4 (first year post-merger). During this
same time interval, the mean STAFF ratings of Acquired hospitals increased by 0.62
percentage points. MOE hospitals increased by 2.57 percentage points in T5 compared to
T3, and by 2.91 percentage points in T6 compared to T3. The Acquired hospitals’ mean
ratings declined by 0.62 percentage points in T5 compared to T4. Acquired hospitals’

STAFF ratings rebounded in T6 with a comparative increase of 1.16 percentage points
over T3.
FEDID testing found the changes in STAFF ratings were significantly different
between MOE hospitals and Acquired hospitals for T4 and T5 (first two years following
the merger or acquisition event, respectively, b= 0.015, p=0.098; b=0.026, p=0.03).
In sum, the findings did not support H3d.
Summary of Results for the Statistical Testing of All 12 Hypotheses
Table 13 provides a summary of testing results. The results supported five of the
12 hypotheses. Seven of the 12 hypotheses were not supported with three of those seven
involving contrary findings: a significant finding but in the opposite direction of what
was posited. Notably, two of the hypotheses (H4b and H4d) were supported by the
findings but not because of any improvement in HCAHPS ratings in the third year
postmerger, but rather because there was no initial impact on ratings after the event.
Table 13
Summary of FEDID Testing Results for the 12 Hypotheses
Hypothesis
Domain
Supported
H1
OVERALL
Yes
H2a
PHYSICIAN
No
H2b
NURSE
Yes
H2c
STAFF
No
H3a
OVERALL
No
H3b
PHYSICIAN
No*
H3c
NURSE
No*
H3d
STAFF
No*
H4a
OVERALL
Yes
H4b
PHYSICIAN
Yes**
H4c
NURSE
No
H4d
STAFF
Yes**
*The opposite relationship was found with MOE hospitals performing significantly better
than Acquired hospitals.
**H4b and H4d were supported but not because of an underlying improvement in
HCAHPS performance in the third year post-merger.

The average rate of change for the OVERALL and NURSE domain ratings
among the Event hospitals compared to the Matched hospitals was significantly lower in
the first 12-24 months post-event. That negative difference persisted in the third year
post-merger for the NURSE domain ratings. However, the rate of change in the
OVERALL ratings among the EHs and MHs in T6 were no longer significantly different.
The EHs did not experience a comparative decline in rate of change in the PHYSICIAN
and STAFF domain ratings during the first 12-24 months following the merger or
acquisition event.
In terms of the hypothesized difference between MOE hospitals and Acquired
hospitals, the opposite relationship was found for three of the four HCAHPS domains
(PHYSICIAN, NURSE, and STAFF). In these three domains, the MOE hospitals
performed significantly better post-merger compared to the Acquired hospitals. There
was no difference between the MOE hospitals and Acquired hospitals in the post-merger
OVERALL ratings.

CHAPTER 5
DISCUSSION
This chapter begins with a restatement of the purpose and background of this
study. Next, there is a general discussion of the major findings, organized around the four
research questions. The third section describes the strengths, weaknesses, and limitations
of this study. The chapter concludes with a review of the implications of this study for
future research, health services managers, policy-makers, and regulators.
Restatement of Study’s Purpose and Theoretical Framework
The U.S. hospital industry has experienced several consolidation waves during the
past 25 years (Maslan & Johnson, 2016). Consequently, most hospital markets in the
United States are considered highly concentrated (National Academy of Social Insurance,
2015). Many economists and health services researchers have examined the impact of
hospital mergers from variety of perspectives, including quality, safety, access, internal
operating costs, pricing, operating margin, and more. No study, however, has evaluated
the effect of hospital mergers on patient experience. This study attempted to fill that gap
by answering the following questions:
1. Prior to merger, do hospitals pursuing a merger have different HCAHPS
ratings compared to similar hospitals that are not pursuing a merger?
2. How does a merger affect HCAHPS performance?
3. Does time play a role in this effect? Does any negative, “merger-related”
effect on HCAHPS ratings dissipate over time? In other words, do HCAHPS
ratings rebound resulting in no difference compared to similar hospitals that
did not complete a merger?

4. Does the type of transaction (merger-of-equals vs. acquisition) moderate this
relationship?
The extant literature on hospital mergers provides strong evidence that
patients/consumers do not receive a quality or safety benefit following a hospital merger
(Bazzoli et al., 2004; Gaynor & Town, 2012; Romano & Balan, 2010; Universal Health
Care Foundation of Connecticut, 2014). Due to increased market power, hospital mergers
oftentimes lead to higher prices for services and higher health insurance premiums
(Gaynor & Town, 2012; Moriya, Vogt, & Gaynor, 2010). The overwhelming body of
research supports the conclusion that hospital mergers are not associated with improved
or enhanced consumer welfare (Bazzoli et al., 2004; Gaynor, 2011; Gaynor & Town,
2012; Town et al., 2006).
Structural Inertia Theory (SIT) and Culture Conflict Theory (CCT) were utilized
to relate the internal, socially disruptive, and distractive impact of a merger on a
hospital’s performance (Figures 4 & 5). Prior research on mergers in other, nonhealthcare
service industries found customer satisfaction scores decline following a merger (Miles &
Rouse, 2011; Swaminathan, Groening, Mittal, & Thomaz, 2013). Research on the
determinants of patient experience found the most influential factors affecting a patient’s
satisfaction with an inpatient episode involved the interaction with physicians, nurses,
and other staff (Boshoff & Gray, 2004; Fowdar, 2005; Tucker & Adams, 2001; Ware et
al., 1978). By integrating SIT and CCT, along with the aforementioned empirical
research, 12 hypotheses were developed that, in general, predicted a negative relationship
between a hospital merger and HCAHPS performance in the 12 to 24 month period
following the merger event. Consistent with the two theories and prior research, merger
disruption and its adverse impact on a hospital’s performance would be temporary (12-24

months) with an expectation of no difference in HCAHPS performance between hospitals
that merged and similar hospitals that did not merge three years after the merger event.
The study also posited that merger type would affect HCAHPS performance and
moderate the merger-related effect, with an expectation that Acquired hospitals would
perform better than MOE hospitals. These hypotheses were based on research on
postmerger acculturation suggesting that imposed acculturation through absorption,
which is the predominant approach used in an acquisition, is more effective than
symbiotic or transformative acculturation methods, which are associated with MOE
situations (Carroll & Harrison, 2004, Ellis & Lamont, 2004; Larsson & Finkelstein,
1999). Additional research on MOEs found the blending of two, previously rival,
organizations operating in the same industry and in the same geographic region triggers
intense post-merger control clashes, power struggles, and political infighting (Devine,
Lamont, & Harris, 2016).
Discussion of the Major Findings – Responses to the Four Research Questions
Question 1: Prior to merger, do hospitals pursuing a merger have different
HCAHPS ratings compared to similar hospitals that are not pursuing a merger?
The HCAHPS ratings of the 99 Event hospitals and the 99 Matched hospitals
were similar and not significantly different for any of the three years leading up to
the merger event (T1, T2 and T3). Consistent with national trends in HCAHPS
ratings, both groups of hospitals increased their mean HCAHPS ratings year-over-
year and at a similar rate during the three-year period leading up to the merger
event. This was expected since the 99 hospital pairs in this study operated in the
same or nearby geographic areas. In most cases, the hospitals in the matched pairs
were directly competing for market-share and patient loyalty from within the same
CBSA or adjacent market. This finding also suggests any strategic, operational, or

financial factors motivating a hospital to pursue a merger did not affect that
hospital’s HCAHPS performance for the three-year time period prior to merger. This
finding also validates the “goodness-of-match” between the 99 Event hospitals and
the 99 Matched hospitals.
Question 2: How does a merger affect HCAHPS performance?
With the exception of the PHYSICIAN Domain and STAFF Domain
composite ratings, the Event hospitals experienced a significantly smaller increase
in their HCAHPS performance in the 12 to 24 month period following the merger
event, when compared to the Matched hospitals’ HCAHPS performance for the
same time period. The year-over-year improvement of HCAHPS ratings for the
OVERALL question and NURSE Domain questions was negatively associated with
Event hospitals.
This finding is supported by this study’s theoretical framework and accompanying
empirical evidence. As depicted in Figure 5, a merger is a radical change within an
organization (Peus, Frey, Gerkhardt, Fischer, & TrautMattausch, 2008). In general,
mergers trigger operational distraction, culture conflict, internal disruption, increased
stress, social upheaval, decreased morale, and anxiety (Marks & Mirvis, 1992). Merger
disruption oftentimes adversely affects organizational performance (Altendorf, 1986;
Bogen & Symmers, 2001; Meeks, 1977; Sinetar, 1981). Job satisfaction levels of hospital
nurses may decline post-merger (Armstrong-Stassen et al., 2001).
Numerous research studies found human interaction (i.e., patient interaction
with nurses, physicians and staff) is the single most influential and predictive
variable on a hospital’s patient experience ratings (Boshoff & Gray, 2004; Fowdar,
2005: Tucker & Adams, 2001; Ware et al., 1978). Furthermore, a large-scale study

involving 98,000 nurses found that nurses’ perceptions of the hospital working
environment had significant effects on HCAHPS performance.
This study’s findings of a merger’s negative effect on the NURSE Domain
composite ratings may be explained by the unique impact that merger disruption
has on the nursing staff and/or the unique response nurses may have to the
organizational disruption. Unlike physicians working within a hospital setting—
who are predominantly independent and/or employed by a separate organization
not under the hospital’s direct control—all hospital-based nurses are
employed/contracted by the hospital with direct supervision and control from
hospital management. They are, therefore, not independent. A hospital-based
nurse’s working environment is determined by the hospital or health system. Since
2010, hospitals in the United States have experienced an increasing
shortage of nurses (Snavely, 2016). Nurses in a hospital going through the social
upheaval and aftermath of a merger may be more willing to express concerns
about the merger knowing they have more job options. Based upon the research
mentioned earlier, how patients perceive their interaction with the nursing staff
significantly affects patients’ perception of their hospital experience (Boshoff &
Gray, 2004; Fowdar, 2005; Tucker & Adams, 2001; Ware et al., 1978). This
study’s findings suggest that nurses experience and respond to merger disruption
differently compared to physicians and non-nursing staff. Consequently, the Event
hospitals’ HCAHPS performance within the NURSE Domain and the OVERALL
rating were adversely affected.
The finding of no difference within the PHYSICIAN Domain composite
ratings may indicate physician behavior and performance was not affected by the
merger. There are varying categories of physicians working within the hospital

setting including independent (private physicians who are solo practitioners or part
of a traditional physician group practice), contracted hospitalists (physicians who
are 100% hospital-based and working for a separate company under contract with
the hospital to provide inpatient care), and employed hospitalists (physicians who
are W-2 employees of the hospital and assigned to provide inpatient care).
This study’s profile of the Event and Matched hospitals did not consider the status of
physicians working within the hospital setting. Therefore, the PHYSICIAN
Domain results cannot be tested by the prevailing physician category
(independent, contracted, and employed) in each hospital.
However, some conjectures can be formed. The PHYSICIAN Domain results
suggest: (1) physicians as a group did not experience a significant level of merger-
related disruption on their work environment, (2) to the extent many physicians
working in a hospital are not employed by or directed by hospital administration,
they are less likely to incur or be the subject of merger disruption, and/or (3)
physicians affected by merger disruption were resilient, thus they were better able to
manage and respond compared to nursing staff.
The finding of no statistically significant difference within the STAFF
Domain is more challenging to explain. All things being equal, one would expect
the post-merger experience of non-nursing staff to be similar to nursing staff.
Although not statistically significant, the STAFF Domain FEDID beta coefficients
for all three post-merger years were negative (T4= -0.002, T5= 0.009, and T6= -
0.009), reflecting a consistently negative gap. The difference between the NURSE
Domain and STAFF Domain findings could be due to the differences in
professional status between the two employee groups. Research conducted by Zell
(2003), Mintzberg (1983), and Merton (1957) found professional bureaucracies to
be especially resistant to organizational change. Nurses are members of a

profession and professional bureaucracy with a certain level of autonomy in their
daily work. To the extent a merger results in organizational disruption and a
specific strain on the merged hospital’s nursing staff, nurses individually and
collectively may perceive a loss of autonomy and, therefore, respond negatively
by resisting the imposed change. Consequently, their job satisfaction levels may
decrease, which, in turn, may affect their job performance and interaction with
patients. Non-nursing staff, many of whom do not hold a professional license,
may not experience the same level of negative response to the merger due to their
lower status and, potentially, greater likelihood of simply accepting organizational
changes. Non-nursing staff may also not have as many alternative job
opportunities as their nurse colleagues; therefore, nonnursing staff may be
reluctant to express concerns or allow their concerns to affect their interactions
with patients. In general, non-professional employees may be more accepting of
merger-related changes and may, therefore, respond in a way that does not affect
patient perception of staff responsiveness.
The significant, negative difference in HCAHPS ratings between Event and
Matched hospitals appeared in T5 or the second year post-merger. FEDID testing
found no difference in HCAHPS performance for T4 or the first year postevent.
This suggests merger-related disruption and social upheaval may not occur
immediately following the merger or acquisition. This may be explained by an
initial “honeymoon effect” as the two organizations celebrate, both internally and
publicly, the merger or acquisition event. After the honeymoon period ends, the
difficult work of blending the two organizations together starts. Operational
changes occur and the reality of the merger and its disruptive effects are felt by
frontline staff.

Question 3: Does time play a role in this effect? In other words, as more times
passes post-merger, do any initial post-merger differences in HCAHPS performance
dissipate over time?
Results of the study suggest dissipation does occur for three of the four
HCAHPS performance metrics. Except for NURSE Domain ratings, the HCAHPS
performance difference between the two groups of hospitals found in the second
post-merger year dissipated by the third post-merger year. Notably, however, there
was no initial (12 to 24 month) post-merger difference in the PHYSICIAN and
STAFF Domain performance between the Event hospitals and Matched hospitals.
However, NURSE Domain ratings did not improve with a finding of
continued significant difference between the Event hospitals and Matched
hospitals in the third year post-merger. This may indicate merger disruption effects
are stronger and/or persist for a longer period among the nursing staff compared to
non-clinical employees. As discussed previously in the answer to Question 2, these
findings suggest the negative impact on nurses and nurses’ experience/response to
the merger disruption effects are worse compared to physicians and the non-
nursing staff. There are several possible explanations.
First, there may some correlation between the level and significance of the
merger disruption effect and the time it takes for that disruptive effect to be resolved
(i.e., the greater the disruption the greater amount of time to dissipate). The second
reason could be tied to how nursing staff experience significant organizational
change nurse and their resilience in dealing with that change. Research on nursing
work environments found a significant, negative relationship between workplace,
environmental stress and nursing performance (i.e., increased stress in the working
environment resulted in decreased nursing performance) (Clegg, 2001). Mergers

increase stress and anxiety levels. Nurses’ response to merger-related disruption and
accompanying stress may be more intense and last longer. One possible explanation
is that nurses, as a group, may not have the same level of resilience and coping
abilities compared to physicians. Note: This study’s post-merger time horizon was
limited to three years, therefore, whether the merger related negative effect on
nurses persisted beyond year three is unknown. Question 4: Does the type of
transaction (Merger-of-Equals vs. Acquired) moderate this relationship?
The findings suggest the effects of a merger on HCAHPS scores does vary
based upon the type of transaction, however, but not in the direction hypothesized.
Except for OVERALL ratings, the study found MOE hospitals performed
significantly better than Acquired hospitals following a merger event.
Why did MOE hospitals perform better? One potential explanation is tied
to the employees’ perception of loss. In an acquisition, employees may interpret
the change as “we have been taken over.” Whereas in an MOE situation, the
perception and prevailing narrative may be more about growth, expansion, and a
positive/promising change. Being acquired involves relinquishing control to the
acquiring entity and a shift in culture. Another factor is how culture is affected and
how acculturation is achieved. In an MOE, there may be an intentional effort to
blend the cultures of the two organizations or establish a new culture with a new
organizational identity. Conversely, in an acquisition, employees of the target
hospital (the hospital being acquired) may perceive the culture change as imposed
or forced. They must give up their culture and organizational identity. This could
lead to more resistance and resentment among the employees.
Weber’s (1996) research sheds light on this phenomenon. In situations
involving an acquisition or takeover (one large firm acquires and completely

absorbs a smaller firm), employees and managers working in the smaller, target
firm may feel unimportant, marginalized, and trivialized. Their feelings of
alienation and discontent may lead them to openly complain to each other and to
customers about the new environment and how things are not the same after being
acquired. In some situations, culture conflict and resentment linger for several
years.
Research on post-merger acculturation methods may offer some insight
into the finding that MOE hospitals performed better post-merger than Acquired
hospitals. The conceptual framework developed by Nahavandi and Malekzadeh
(1988) identified four approaches for the successful blending of two organizations.
Two of those four are commonly used in MOE situations:
symbiotic (intentional efforts to combine the best cultural elements of the two
organizations) and transformation (establishing a completely new culture). This study’s
findings may indicate senior leaders and boards involved with the 44
MOE hospitals made acculturation an important element of pre-merger planning. This
study did not evaluate or classify post-merger acculturation. However, the findings
suggest the 44 MOE hospitals may have done a better job developing and
implementing a post-merger culture-blending plan as compared to the 55
Acquired hospitals.
Another interesting takeaway from the MOE vs. Acquired comparison is the
difference in the PHYSICIAN Domain, with the MOE hospitals having
significantly better post-merger PHYSICIAN Domain ratings compared to the
Acquired hospitals. Note that no difference was found in the PHYSICIAN
Domain ratings in the aggregate groups: the 99 Event hospitals compared to the
99 Matched hospitals. Post-merger, the PHYSICIAN Domain ratings of the
Acquired hospitals was unchanged, meaning no improvement (Table 8). However,

the PHYSICIAN Domain ratings of the MOE hospitals increased significantly in
the first year post-merger.
There are several possible explanations. MOE situations may be more
likely to involve physicians in both the merger planning and post-merger
execution. Since an MOE is an agreement among two hospitals or health systems
to combine their assets into a new entity, leaders of the two organizations may
take more deliberate steps to engage physicians earlier in the process and, thereby,
achieve a higher level of physician buy-in. The opposite may occur in an
acquisition situation. Leadership of the target hospital may be less inclined to open
the process and negotiations to the medical staff. Physicians in an acquisition
situation may not know about the deal until late in the process or until the deal is
finalized. This low engagement and lack of transparency, both before and after the
transaction is concluded, could trigger a significant negative reaction among the
medical staff.
Another factor involves loss of control. Prominent physicians in the target hospital
may have enjoyed substantial control and influence in the hospital operations prior to the
acquisition. Post-acquisition, the new owner may change leadership at the acquired
hospital and centralize power and decision-making, thus significantly reducing the local
physicians’ influence and control. This loss of control, coupled with the low engagement
and lack of transparency, could cause overt opposition and animosity between the
medical staff and the acquiring entity. The combination of resentment, anger, and loss
would likely, adversely affect the hospital environment, physician commitment and
performance, and how patients perceive their interactions with physicians.

Strengths and Weaknesses/Limitations
This study has several strengths. First, the sample size of 198 hospitals (99 Event
hospitals and 99 Matched hospitals) enhanced the power of the study. The majority of the
published, empirical research on hospital mergers conducted in the past 30 years involved
a significantly smaller sample size of hospitals. Next, the study included hospitals from
diverse geographic areas, including 50 CBSAs, 15 rural areas, and 33 states. Third, the
study included mergers that occurred during a five-year time period (2009 through 2013),
which was one of the more active hospital merger waves in the past 30 years. Fourth, the
study had access to a standardized (and consistently used) tool for measuring and
reporting patient experience (i.e., the HCAHPS assessment). Fifth, the 99 Event hospitals
and the 99 Matched hospitals had equivalent HCAHPS ratings for the three-year time
period leading up to the merger event, which enhances the ability to correlate differences
in the study’s outcome variable (post-event HCAHPS performance) to the predictor
variable (merger status of the 198 hospitals in the study). Last, with a few exceptions, the
Event hospitals and the Matched hospitals were well-matched geographically and by size
with an acceptable level of equivalence (Table 1).
The study also has some notable weaknesses and limitations. First, although the
99 pairwise matches were, in aggregate, equivalent, some of the individual pairs were
weaker matches. As discussed in the Methods chapter, a few discretionary exceptions
were made to allow several pairs to remain in the study, despite some geographic, size, or
other differences. The fact that numerous geographic markets experienced a high level of
mergers during the study’s time period (2009-2013) limited the ability to locate suitable
matches for many Event hospitals, resulting in the removal of those hospitals from this
study. Similarly, many of the merger events that occurred in 2009 were eliminated from

the study due the lack of HCAHPS ratings for three years prior (in 2006). These
necessary exclusions could have affected the results of this study.
Financial performance, both pre- and post-merger, could have affected HCAHPS
performance. This study’s results are limited by not controlling for a hospital’s financial
performance (i.e., operating margin). Although most not-for-profit health systems and
publicly traded for-profit hospital companies publicly report their financial statements on
a consolidated basis, operating margins by individual NPI# hospital are not publicly
available. Since individual hospitals were the subject of this study, it was not possible to
control for financial performance. Therefore, it is unknown whether or not an individual
hospital’s financial performance impacted its HCAHPS ratings.
The MOE vs. Acquired hospital analysis and findings were limited by the fact that
a several large health system mergers represented most of the MOE hospitals. For
example, 25% (11 of 44) of the MOE hospitals in this study were involved with one
Texas merger: Baylor’s merger with Scott & White. This one merger could skew the
MOE hospitals’ collective performance. Consequently, interpretation of the MOE vs.
Acquired hospital FEDID testing results should take this into consideration.
The findings support the general hypothesis of a negative association between
hospital mergers and HCAHPS ratings; however, no causal relationship could be
concluded. Although some significant negative relationships were found, those
relationships may be due to mediating and/or moderating variables that were not included
in this study.
Implications for Future Research
There are several important implications for future research. Since the theoretical
framework and literature review focused on a merger’s impact on the internal working
environment and culture, future researchers should consider quantifying pre- and

postmerger culture and acculturation factors as possible mediators of post-merger
disruption. This research could increase understanding of how physicians, nurses, and
other hospital staff respond to different cultures and acculturation techniques post-merger.
Similarly, future research could be conducted to examine the relationship between
hospital mergers and physician satisfaction, nurse satisfaction, and general staff
satisfaction. As noted in the discussion about this study’s weaknesses, it is unknown
whether the post-merger difference in HCAHPS performance between the Event and
Matched hospitals involved changes in physician, nurse, and staff satisfaction.
Another implication for future research involves the discordant findings with the
PHYSICIAN Domain and NURSE Domain ratings. Future research could focus on
physicians in a merger environment to better understand how physicians experience and
respond to a merger event. For the NURSE Domain, future research could examine why
these ratings did not improve three years following the merger as was found with the
OVERALL ratings and STAFF Domain ratings.
How a hospital merger affects patient expectations is another potential area for
future research. In many cases, a hospital merger involves community input and support.
Board members, physicians, and community leaders interested in preserving access to
care may engage the public for support of a proposed merger. Is it possible that
community engagement and public support for a hospital merger changes patient
expectation? Do patients expect more from the hospital following a merger? Do patients
associate a merger with better hospital performance? Future research could examine the
relationship between a hospital merger and the effect on patient expectations.
Contrary to previous research involving non-healthcare mergers, and opposite of
the four applicable hypotheses, Acquired hospitals performed worse than MOE hospitals.
Future qualitative and quantitative research could examine these merger types to better

explain this study’s findings. Are there certain pre-event characteristics (e.g., market size,
scope of services, employee satisfaction, financial performance) that are associated with
Acquired hospitals? Are there differences in how post-merger acculturation is done
between Acquired and MOE hospitals? What is the role of physicians in the pre-event and
post-event planning and decision-making? Do hospitals that are acquired have more
reduction in services post-event compared to MOE hospitals? Do hospitals that are
acquired experience more job losses compared to MOE hospitals? These and many other
questions could be explored in future research on how hospital merger type affects
postevent performance.
Finally, future research could extend the post-merger time horizon beyond three
years to five or more years to determine when, if ever, the merger-related, negative
effects on HCAHPS performance fully dissipate (i.e., there is no difference in HCAHPS
performance between Event hospitals and Matched hospitals).
Implications for Health Services Leaders, Hospital Boards, Policy-Makers &
Regulators
The findings from this research provide a new perspective and additional answers
to the question: What value does a hospital merger generate for the patients and
communities it serves? For executives and board members considering a merger or
acquisition, the results of this study can be used to guide pre-merger discussions and post-
merger implementation. Knowing that a merger can cause social upheaval and, therefore,
may have a negative effect on HCAHPS performance, leaders may consider
implementing additional initiatives to moderate post-merger culture conflict and
mergerrelated disruptions among physicians, nurses, and general staff. Hospitals and
health systems pursuing a merger should also pay special attention to and make additional
investments in the nursing staff.

Healthcare policy-makers and regulators, at both the federal and state level, could
use this study to develop targeted requirements for hospitals and health systems seeking
government approval for a merger or acquisition. Specifically, the findings from this
study could open a constructive dialogue about the importance of patient experience and
HCAHPS performance as a critical part of the evaluation of the merger’s impact on
consumer welfare. To that end, regulators should consider holding hospitals and health
systems accountable for achieving and maintaining minimum levels of post-merger
HCAHPS performance. Furthermore, additional oversight and monitoring may be needed
for acquired hospitals.
Conclusion
This quasi-experimental study aimed to examine and evaluate the relationship
between hospital mergers and patient experience. This was the first study on hospital
mergers with patient experience as the variable of interest. The study sought to extend a
large body of prior research on hospital mergers, which found little to no improvement in
consumer welfare following a merger event. In general, the evidence on hospital mergers
suggests neutral to negative effects on quality, safety, and pricing.
This study found that hospital mergers do not result in improved patient
experience performance. To the contrary, compared to similar hospitals that did not
merge, the rate of change of OVERALL ratings and NURSE Domain ratings of merged
hospitals declined compared to similar hospitals that did not merge. This study also found
a significant difference in HCAHPS performance based upon merger type: MOE
hospitals compared to Acquired hospitals.
To optimize consumer welfare and deliver more benefit to patients, health services
researchers, healthcare leaders, health policy-makers, and government regulators should

consider this study’s findings in light of the continued consolidation of hospitals and
health systems in the United States.

