



1
MUSCLE FATIGUE IN CEREBRAL PALSY: ITS MEASUREMENT AND CONNECTION
TO FUNCTIONAL LIMITATIONS
Chapter 1: introduction
Cerebral palsy (CP) describes a collection of disorders “of the development of movement
and posture, causing activity limitation, that are attributed to non-progressive disturbances that
occurred in the developing fetal or infant brain” (Bax et al., 2005). CP is not a disease, per se,
but rather, a descriptive term that describes a heterogeneous group of children who often
manifest with chronic motor impairment. Although variability exists with respect to the degree of
impairments individuals with CP may exhibit, common impairments include loss of selective
motor control, spasticity, muscle weakness, co-contraction, and contractures. In turn, these
impairments can lead to activity restrictions such as difficulty in walking and other activities of
daily living, with many patients experiencing worsening disability throughout the lifespan.
Studies over the last 10 to 15 years have documented a gradual onset of newly
recognized problems in adults with CP, such as fatigue, musculoskeletal pain, and deterioration
of functional skills (Andersson & Mattsson, 2001; Bottos, Feliciangeli, Sciuto, Gericke, &
Vianello, 2001; Cathels & Reddihough, 1993; Gajdosik & Cicirello, 2001; Jahnsen, Villien,
Egeland, Stanghelle, & Holm, 2004; Jahnsen, Villien, Stanghelle, & Holm, 2003; Murphy,
Molnar, & Lankasky, 1995; Pimm, 1992). These problems manifest in adolescence and early
adulthood and have consequences for activities and participation in work and social situations.
Furthermore, these studies provide evidence of the progression of secondary impairments in CP
and the need for targeted interventions throughout the life span, despite the non-progressive
brain lesion
Physical fatigue, in particular, has been identified as a significant impairment in adults
with CP compared with the general population and has been significantly associated with
deterioration of functional skills, bodily pain, limitations in physical and emotion role function,
and low life satisfaction (Jahnsen et al., 2003). In fact, adults with CP report fatigue as a main
cause of the deterioration or cessation of their walking ability (Bottos et al., 2001; Jahnsen et al.,

2
2004; Murphy et al., 1995). Murphy et al. (1995) reported that 75% of subjects ceased to walk
by the age of 25 due to fatigue and inefficiency of ambulation. Jahnsen et al. (2004) reported that
44% of subjects had deterioration of walking due to fatigue, pain, and lack of adapted physical
activity. However, fatigue was assessed subjectively in these studies through the use of
questionnaires and interviews and did not attempt to differentiate among cardiorespiratory
fatigue (e.g. heart beating too fast or person feeling out of breath), neural or psychological
fatigue (increased sense of effort or feeling as if muscles are going to ‘give out’) or local muscle
fatigue (muscles cannot produce as much or any force as they could at onset of task).
Fatigue may be studied as a subjective symptom or the state of being fatigued.
Conversely, fatigue can also be studied as an objective process with measurable signs, such as
reduction in peak torque or work, and is often referred to as muscle fatigue (Bigland-Ritchie,
Johansson, Lippold, & Woods, 1983). However, the two do not always correlate (Iriarte & de,
1998; Sharma, Kent-Braun, Mynhier, Weiner, & Miller, 1995). The term “fatigue” as a
subjective phenomenon has been used to describe a multitude of mental and physical symptoms
and is often confused with other symptoms, such as weakness (Schwid, Covington, Segal, &
Goodman, 2002). For example, a question in the Fatigue Questionnaire (Chalder et al., 1993)
used in the Jahnsen et al. (2003) study reads “Do you have less strength in your muscles?”
Another question reads “Do you feel weak?” Therefore, these self-report questionnaires are not
adequate in the assessment of the objective or physical signs of fatigue (Schwid et al., 2002).
Background Information
Because of the broad use of the term fatigue, it is important to operationally define
fatigue. Muscle fatigue, or fatigability, will be defined as a reduction in the force-generating
capacity of the neuromuscular system, which occurs during sustained activity (Bigland-Ritchie et
al., 1983). Muscle endurance, on the other hand, is resistance to fatigue or the ability to

3
withstand fatigue. These terms are often used interchangeably throughout the literature with
muscle endurance tests often employed to assess muscle fatigue.
The first published test of muscle fatigue in children with neuromuscular disease was
measured as the length of time that the subject could hold the extended lower extremity 45
degrees off of the ground while in a supine position (Hosking, Bhat, Dubowitz, & Edwards,
1976). Although this test was able to discriminate between children with and without
neuromuscular disease, it was very difficult to standardize and did not show sufficient
reproducibility to be recommended for future testing.
Other attempts to measure cardiorespiratory endurance in children with CP employed
physiological measures of energy expenditure, such as oxygen consumption, heart rate,
perceived exertion, and other measures of cardiorespiratory function (Hoofwijk, Unnithan, &
Bar-Or, 1995; Rose, Haskell, & Gamble, 1993; Unnithan, Dowling, Frost, & Bar-Or, 1996). It
has been well documented that children and adolescents with CP have lower VO2max than able-
bodied peers as assessed during tasks, such as lower extremity cycling (Lundberg, 1978) and
treadmill ambulation (Hoofwijk et al., 1995; Rose et al., 1993). However, these authors
independently suggested that additional factors other than cardiorespiratory were responsible for
the limitations in the respective activities. Lundberg (1978) and Hoofwijk et al. (1995) suggested
that spasticity may have decreased venous return and inhibited muscle lactate clearance during
exercise, thereby increasing local muscle fatigue and leading to a decrease in VO2max values.
Furthermore, because some believe that movement in children with CP is often accomplished
through discrete bursts of activity, it has been suggested that aerobic function is unlikely to be a
limiting factor in the ability of a child with CP to perform activities (Unnithan, Clifford, & Bar-
Or, 1998). Rather, anaerobic power has been considered to be the better measure of functional
capacity in people with neuromuscular diseases, including CP (Unnithan et al., 1998).

4
Several investigators have studied muscle endurance from an anaerobic perspective in
children and adolescents with CP by means of the Wingate Anaerobic Cycling Test (WAnT).
The WAnT is a widely used, validated measure of anaerobic performance (Bar-Or, Dotan, &
Inbar, 1977). It is reliable in both adults and children (Bar-Or, 1987) as well as in children with
neuromuscular diseases, including those with CP (Tirosh, Bar-Or, & Rosenbaum, 1990). It is a
30-second test, during which the subject pedals at maximal speed against a predetermined
constant resistance based on body weight. From this test, peak power and mean power are
calculated. Peak power is a measure of explosiveness and is moderately correlated with the
percentage of fast twitch fibers in the vastus lateralis muscle (Bar-Or et al., 1980). Peak power is
calculated as the product of flywheel resistance x number of revolutions x distance per revolution
divided by time (usually 3 second sampling period). Proponents of anaerobic testing purport to
measure muscle endurance by measuring mean power of the lower extremities during the WAnT.
Mean power is the average of all power values measured at each sampling period. Results from
these studies indicate that peak muscle power and mean power, as a measure of muscle
endurance, are markedly deficient in people with CP (Parker, Carriere, Hebestreit, & Bar-Or,
1992; Parker, Carriere, Hebestreit, Salsberg, & Bar-Or, 1993; Tirosh et al., 1990). However, this
test cannot differentiate between right and left extremities nor can it differentiate among muscle
groups; therefore, it is a non-specific, gross physiologic measurement of endurance.
Furthermore, the measurement of mean power does not reflect the decline in force during
sustained activity. Rather, it is an absolute measure that reflects the average level of
explosiveness or power. Mean power has been directly correlated (r = 0.75) to relative fast twitch
fiber size, where higher mean power equals higher endurance and preponderance of fast twitch
fibers (Bar-Or et al., 1980). It is well established that fast twitch fibers are more fatigable;
therefore, if mean power is a measure of muscle endurance, it does not correlate with our current

5
understanding of muscle physiology. We propose that this measurement does not reflect the
decline in the force-generating capacity of the muscle, but rather reflects average power
production throughout the test.
Isokinetic dynamometry, on the other hand, has the ability to isolate a single muscle
group under controlled conditions with stabilization of other joints, thus providing a measure of
localized muscle fatigue. Reliable isokinetic fatigue protocols have been established for children
(De Ste Croix, Armstrong, & Welsman, 2003), adults (Pincivero, Lephart, & Karunakara, 1997),
and the neurologically impaired (Lambert, Archer, & Evans, 2001). However, to date, there are
no studies that have quantitatively assessed localized muscle fatigue via isokinetic or isometric
means in individuals with CP. The most commonly assessed muscle groups in these studies are
the knee flexors and extensors. Clinically, it is important to study lower extremity muscles,
particularly of the knee flexors and extensors, because they have been shown to be correlated to
motor function in people with CP (Damiano & Abel, 1998; Damiano, Martellotta, Sullivan,
Granata, & Abel, 2000; MacPhail & Kramer, 1995). Furthermore, it is important to study more
than one muscle group because muscle characteristics such as size, fiber type distribution, fiber
arrangement, recruitment and rate coding strategies differ considerably across muscle groups.
These differences may become even more exaggerated in persons with CP because factors like
spasticity, weakness, and selective motor control may affect different muscle groups to varying
degrees.
Experiments
The World Health Organization’s International Classification of Functioning, Disability
and Health (ICF) model was used as a framework in the investigation of muscle fatigue within
the population of CP (World Health Organization, 2001). The ICF is a classification of health
related domains that describe body functions and structures, activities, and participation in an

6
effort to understand and measure health outcomes. Three levels of human functioning are
classified by ICF: functioning at the level of body or body part (body functions and structures),
the whole person (activities), and the whole person in a social context (participation). The formal
definitions of the components of the ICF are provided in Table 1.1.
Table 1.1. Definitions of the components of the World Health Organization’s ICF model (2001)
Terms Definition
Body functions Physiological functions of body systems (including psychological
components)
Body structures Anatomical parts of the body such as organs, limbs, and their
components
Impairments Problems in body function or structure such as a significant
deviation or loss
Activity Execution of a task or action by an individual
Activity Limitations Difficulties an individual may have in executing activities
Participation Involvement in a life situation
Participation Limitations Problems an individual may experience in involvement in life
situations
Based on this model, three experiments have been designed to further explore the
measurement of muscle fatigue of the knee flexors and extensors; possible contributing factors to
muscle fatigue at the body function level; activity limitations and participation restrictions
associated with muscle fatigue; and the relationship of muscle fatigue to aspects of psychosocial
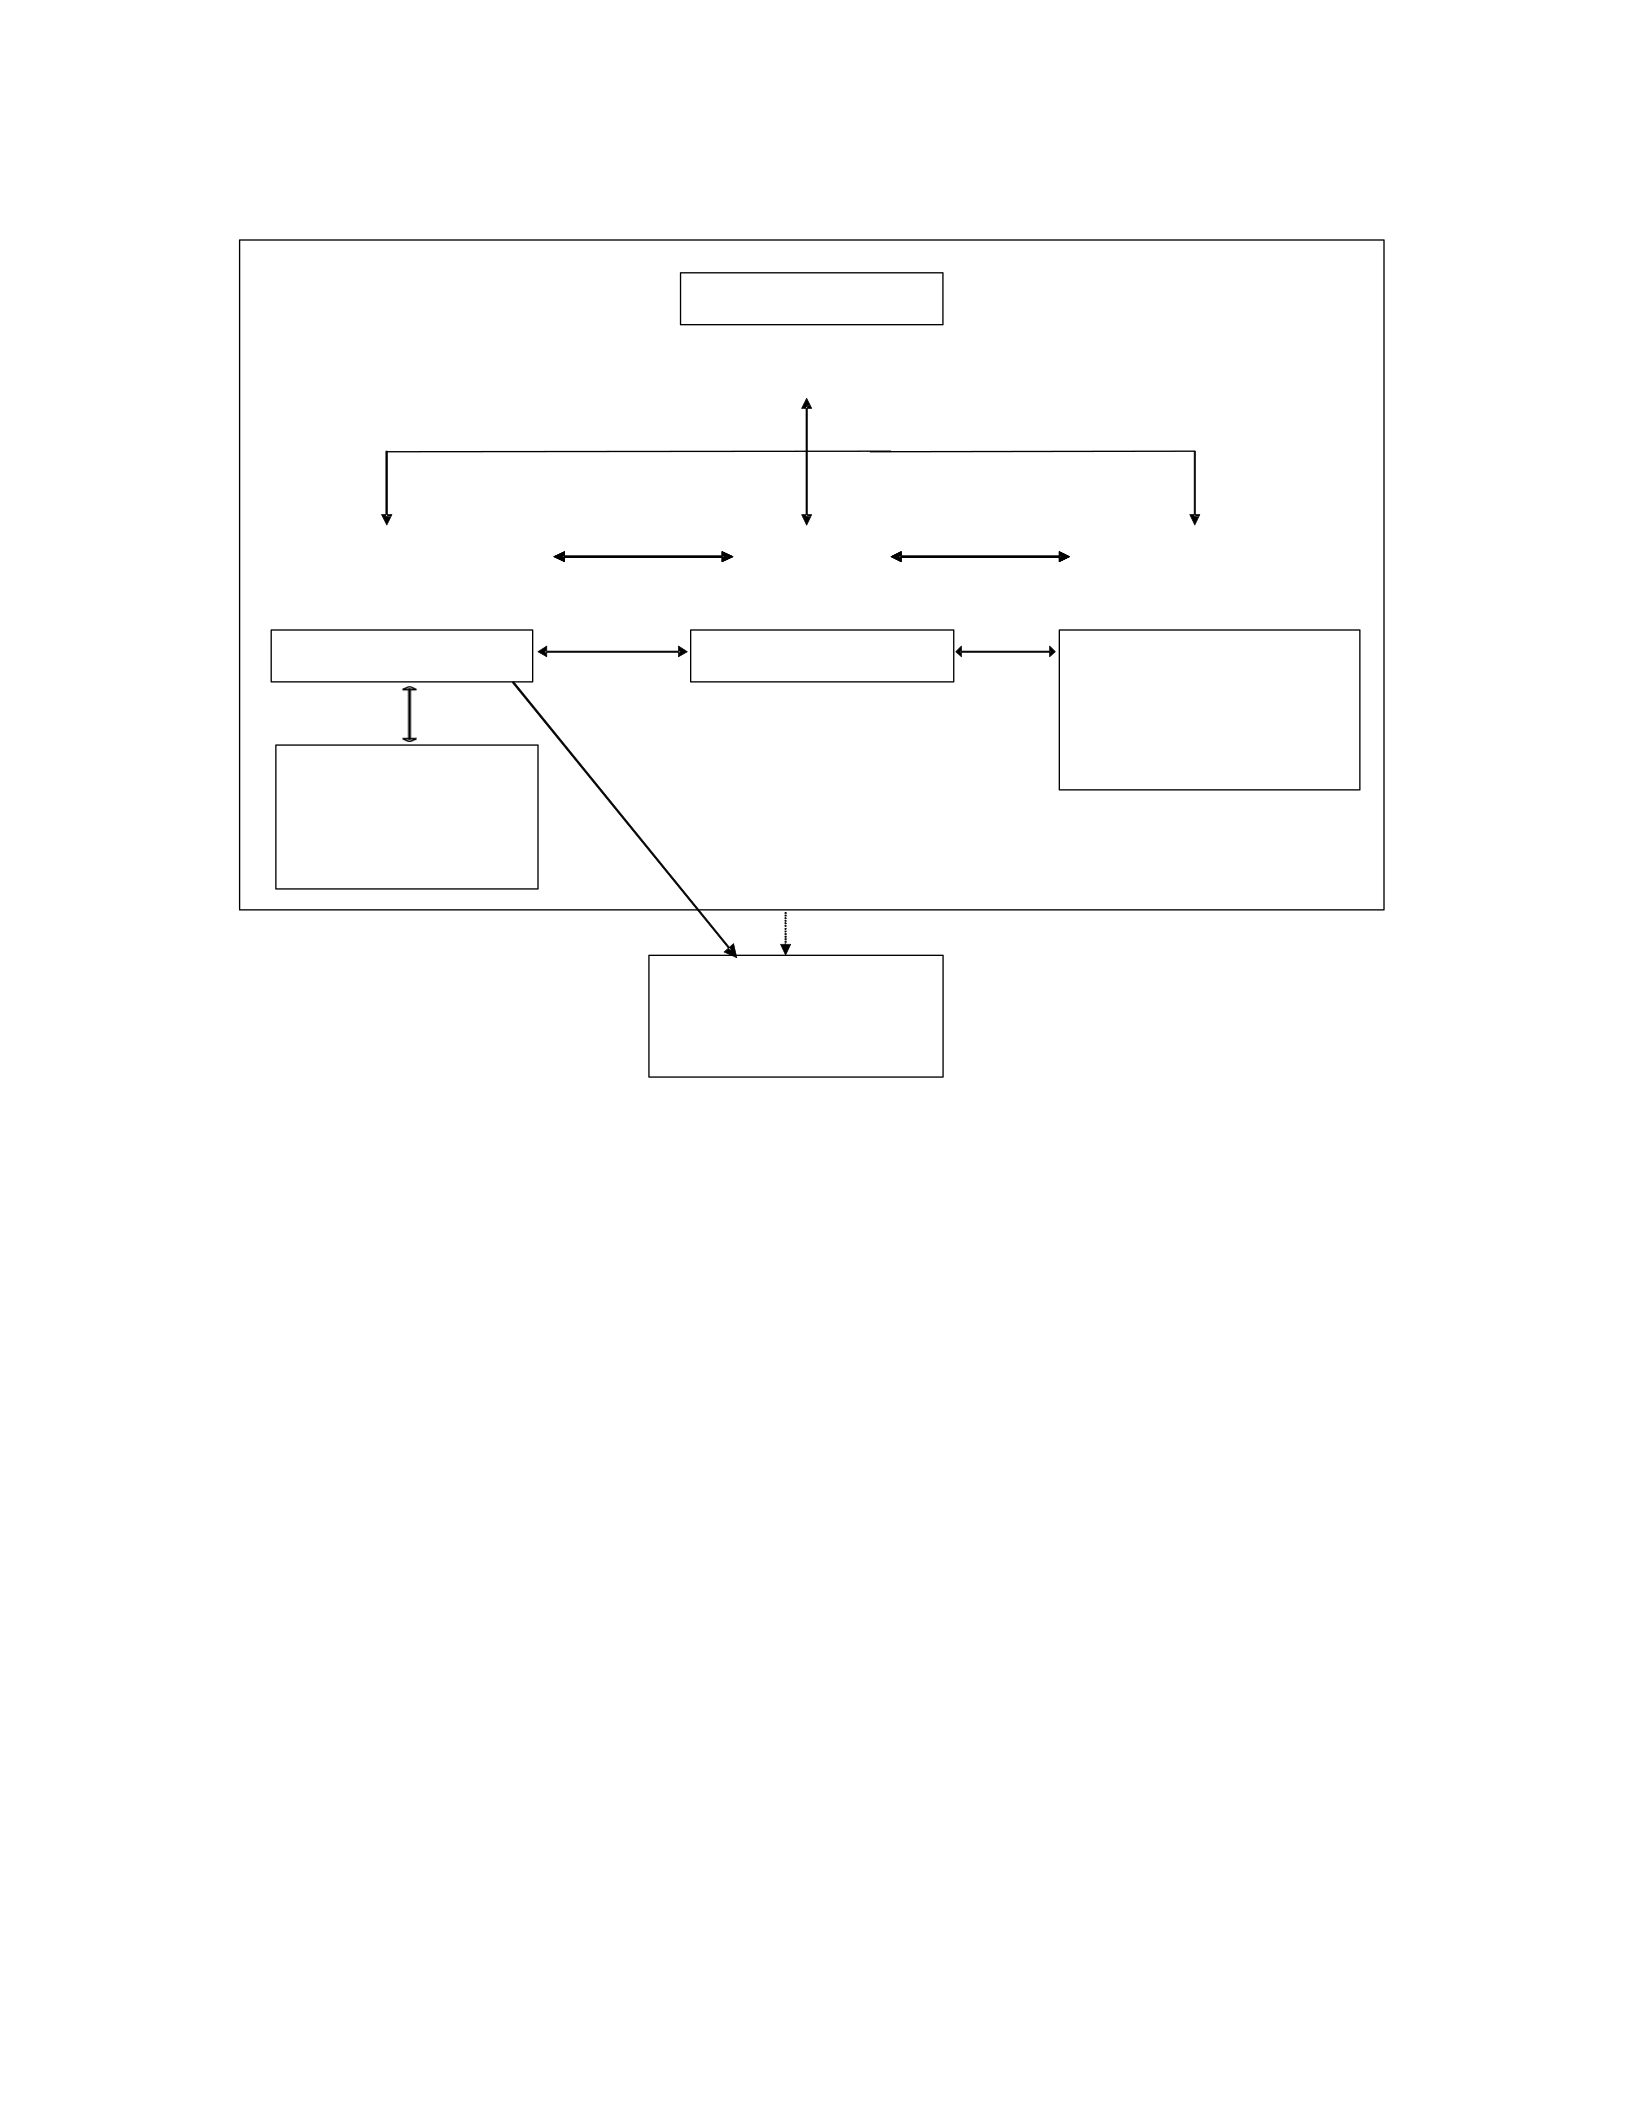
well-being. Figure 1.1 illustrates the experiments within the context of the ICF model.
Despite the evidence that fatigue is a problem in this population, there are no studies that
have quantitatively assessed muscle fatigue. Therefore, the feasibility of an isokinetic muscle
fatigue protocol for the knee flexors and extensors in ambulatory children with CP was
investigated in Chapter 2 (experiment 1). In addition, the reliability of 3 fatigue measurement
parameters was reported.
7
“Psychosocial well-being”
Figure 1.1. Illustration of the WHO ICF (2001) framework for the investigation of muscle
fatigue within the health condition of CP; possible contributing factors to fatigue at the body
function level, which are spasticity, stiffness, weakness, and cocontraction; activity limitations;
participation restrictions; and the relationship of muscle fatigue to aspects of psychosocial well-
being. It should be noted that psychosocial well-being is not a part of the ICF model.
In Chapter 3 (experiment 2), the protocol established in Chapter 1 was utilized to
investigate whether muscle fatigue of the knee flexors and extensors was greater in individuals
with CP compared to those without disability. Furthermore, as illustrated in Figure 1.1, the
relationship of muscle fatigue (body functions) in individuals with CP (health condition) to
activities (walking velocity); participation in sports and physical function; transfers and basic
mobility; and aspects of psychosocial well-being such as happiness, satisfaction, and
pain/comfort, was investigated.
Health condition
Body structures
and functions
Activity Participation
Happiness
Pain/Comfort
Satisfaction
Spasticity
Weakness Stiffness
Cocontraction
Sports & Physical
Function
Transfers & Mobility
Walking velocityFATIGUE
Cerebral Palsy

8
In Chapter 4 (experiment 3) the relationship of muscle fatigue (body functions) to other
impairments at the body function level were investigated to determine whether these factors
contributed significantly to the level of muscle fatigue observed in our subjects with CP. CP is a
multifaceted disorder and as such, complex interrelationships exist among upper motor neuron
lesion impairments. The relationships among muscle fatigue and other impairments at the body
function level are important in the understanding of fatigue, as these impairments may, in fact,
contribute directly or indirectly to the level of muscle fatigability. As a result, four possible
contributors to the level of muscle fatigability at the impairment/body function level were
investigated and are presented in Figure 1.1: spasticity, weakness, co-contraction, and stiffness.
Finally, synthesis of the conclusions presented in these chapters is presented in Chapter 5.
Reference List
Andersson, C. & Mattsson, E. (2001). Adults with cerebral palsy: a survey describing
problems, needs, and resources, with special emphasis on locomotion. Dev.Med.Child
Neurol., 43, 76-82.
Bar-Or, O. (1987). The Wingate Anaerobic Test - An Update on Methodology, Reliability and
Validity. Sports Medicine, 4, 381-394.
Bar-Or, O., Dotan, R., & Inbar, O. (1977). 30-Sec All-Out Ergometric Test - Its Reliability and
Validity for Anaerobic Capacity. Israel Journal of Medical Sciences, 13, 326-327.
Bar-Or, O., Dotan, R., Inbar, O., Rothstein, A., Karlsson, J., & Tesch, P. (1980). Anaerobic
Capacity and Muscle Fiber Type Distribution in Man. Int.J.Sports Med., 1, 82-85.
Bax, M., Goldstein, M., Rosenbaum, P., Leviton, A., Paneth, N., Dan, B. et al. (2005). Proposed
definition and classification of cerebral palsy, April 2005. Dev.Med.Child Neurol., 47,
571-576.
Bigland-Ritchie, B., Johansson, R., Lippold, O. C., & Woods, J. J. (1983). Contractile speed and
EMG changes during fatigue of sustained maximal voluntary contractions.
J.Neurophysiol., 50, 313-324.
Bottos, M., Feliciangeli, A., Sciuto, L., Gericke, C., & Vianello, A. (2001). Functional status of
adults with cerebral palsy and implications for treatment of children. Dev.Med.Child
Neurol., 43, 516-528.

9
Cathels, B. A. & Reddihough, D. S. (1993). The health care of young adults with cerebral palsy.
Med.J.Aust., 159, 444-446.
Chalder, T., Berelowitz, G., Pawlikowska, T., Watts, L., Wessely, S., Wright, D. et al. (1993).
Development of a fatigue scale. J.Psychosom.Res., 37, 147-153.
Damiano, D. L. & Abel, M. F. (1998). Functional outcomes of strength training in spastic
cerebral palsy. Arch.Phys.Med.Rehabil., 79, 119-125.
Damiano, D. L., Martellotta, T. L., Sullivan, D. J., Granata, K. P., & Abel, M. F. (2000). Muscle
force production and functional performance in spastic cerebral palsy: relationship of
cocontraction. Arch.Phys.Med.Rehabil., 81, 895-900.
De Ste Croix, M. B. A., Armstrong, N., & Welsman, J. R. (2003). The reliability of an isokinetic
knee muscle endurance test in young children. Pediatric Exercise Science, 15, 313-323.
Gajdosik, C. G. & Cicirello, N. (2001). Secondary conditions of the musculoskeletal system in
adolescents and adults with cerebral palsy. Phys.Occup.Ther.Pediatr., 21, 49-68.
Hoofwijk, M., Unnithan, V., & Bar-Or, O. (1995). Maximal treadmill performance of children
with cerebral palsy. Pediatric Exercise Science, 7, 305-313.
Hosking, J. P., Bhat, U. S., Dubowitz, V., & Edwards, R. H. (1976). Measurements of muscle
strength and performance in children with normal and diseased muscle. Arch.Dis.Child,
51, 957-963.
Iriarte, J. & de, C. P. (1998). Correlation between symptom fatigue and muscular fatigue in
multiple sclerosis. Eur.J Neurol., 5, 579-585.
Jahnsen, R., Villien, L., Egeland, T., Stanghelle, J. K., & Holm, I. (2004). Locomotion skills in
adults with cerebral palsy. Clin.Rehabil., 18, 309-316.
Jahnsen, R., Villien, L., Stanghelle, J. K., & Holm, I. (2003). Fatigue in adults with cerebral
palsy in Norway compared with the general population. Dev.Med.Child Neurol., 45, 296-
303.
Lambert, C. P., Archer, R. L., & Evans, W. J. (2001). Muscle strength and fatigue during
isokinetic exercise in individuals with multiple sclerosis. Med.Sci.Sports Exerc., 33,
1613-1619.
Lundberg, A. (1978). Maximal aerobic capacity of young people with spastic cerebral palsy.
Dev.Med.Child Neurol., 20, 205-210.
MacPhail, H. E. & Kramer, J. F. (1995). Effect of isokinetic strength-training on functional
ability and walking efficiency in adolescents with cerebral palsy. Dev.Med.Child Neurol.,
37, 763-775.
Murphy, K. P., Molnar, G. E., & Lankasky, K. (1995). Medical and functional status of adults
with cerebral palsy. Dev.Med.Child Neurol., 37, 1075-1084.

10
Parker, D. F., Carriere, L., Hebestreit, H., & Bar-Or, O. (1992). Anaerobic endurance and peak
muscle power in children with spastic cerebral palsy. Am.J.Dis.Child, 146, 1069-1073.
Parker, D. F., Carriere, L., Hebestreit, H., Salsberg, A., & Bar-Or, O. (1993). Muscle
performance and gross motor function of children with spastic cerebral
palsy. Dev.Med.Child Neurol., 35, 17-23.
Pimm, P. (1992). Cerebral palsy; a non progressive disorder? Educational and Child Psychology,
9, 27-33.
Pincivero, D. M., Lephart, S. M., & Karunakara, R. A. (1997). Reliability and precision of
isokinetic strength and muscular endurance for the quadriceps and hamstrings.
Int.J.Sports Med., 18, 113-117.
Rose, J., Haskell, W. L., & Gamble, J. G. (1993). A comparison of oxygen pulse and respiratory
exchange ratio in cerebral palsied and nondisabled children. Arch.Phys.Med.Rehabil., 74,
702-705.
Schwid, S. R., Covington, M., Segal, B. M., & Goodman, A. D. (2002). Fatigue in multiple
sclerosis: current understanding and future directions. J.Rehabil.Res.Dev., 39, 211-224.
Sharma, K. R., Kent-Braun, J., Mynhier, M. A., Weiner, M. W., & Miller, R. G. (1995).
Evidence of an abnormal intramuscular component of fatigue in multiple sclerosis.
Muscle Nerve, 18, 1403-1411.
Tirosh, E., Bar-Or, O., & Rosenbaum, P. (1990). New muscle power test in neuromuscular
disease. Feasibility and reliability. Am.J.Dis.Child, 144, 1083-1087.
Unnithan, V. B., Clifford, C., & Bar-Or, O. (1998). Evaluation by exercise testing of the child
with cerebral palsy. Sports Med., 26, 239-251.
Unnithan, V. B., Dowling, J. J., Frost, G., & Bar-Or, O. (1996). Role of cocontraction in the
O2 cost of walking in children with cerebral palsy. Med.Sci.Sports Exerc., 28, 1498-
1504.
World Health Organization (2001). International Classification of Functioning, Disability and
Health. Geneva: World Health Organization.

11
CHAPTER 2: A FEASIBLE AND RELIABLE MUSCLE FATIGUE ASSESSMENT
PROTOCOL FOR INDIVIDUALS WITH CEREBRAL PALSY
Introduction
Lower extremity muscle strength, particularly of the knee flexors and extensors, has been
shown to be correlated to motor function in cerebral palsy (CP) (Damiano & Abel, 1998;
Damiano, Martellotta, Sullivan, Granata, & Abel, 2000; MacPhail & Kramer, 1995). As a result,
routine isokinetic and isometric measurements of strength are becoming increasingly common in
this population. While the importance of maintaining muscle strength is being increasingly
recognized for those with chronic motor disabilities such as CP, recent studies have indicated
that ‘fatigue’ is an even more frequent complaint of adults with CP and has been cited as a major
limiting factor in diminished ambulatory capacity in early to middle adulthood (Jahnsen, Villien,
Egeland, Stanghelle, & Holm, 2004). Corroborating this subjective complaint is objective
evidence that cardiorespiratory endurance is reduced in individuals with CP (Lundberg, 1976;
Lundberg, 1978). However, while muscle endurance, or resistance to fatigue, is known to be an
important component of normal muscle performance, a search of the medical literature to date
revealed no investigations of fatigue at the muscle level in CP. Muscle fatigue is defined as a
reduction in the force-generating capacity of the neuromuscular system, which occurs during
sustained activity (Bigland-Ritchie, Johansson, Lippold, & Woods, 1983). Muscle endurance is
defined as the ability to withstand fatigue. The term muscle endurance is often used in the
literature as the antonym, or positive, of muscle fatigue, similar to the use of strength vs.
weakness.
The first reported test of muscle fatigue in children with neuromuscular diseases was by
Hosking, Bhat, Dubowitz, and Edwards (1976). In their protocol, the length of time the lower leg
could be held out straight with the hip flexed to 45 degrees and the head at 45 degrees above the
horizontal were recorded with the subject in the supine position. Although this test was able to

12
discriminate between children with and without neuromuscular disease, it did not show sufficient
reproducibility to be recommended for future testing.
Reported measures of cardiorespiratory endurance in children with CP have included
physiological assessments of energy expenditure, oxygen consumption, heart rate, and subjective
reports of perceived exertion among other measures of cardiorespiratory function (Lundberg,
1976; Rose, Haskell, & Gamble, 1993). Others have studied endurance from an aerobic
(Lundberg, 1978) versus anaerobic perspective (Parker, Carriere, Hebestreit, & Bar-Or, 1992).
However, these cardiorespiratory assessments are distinctly different both physiologically and
methodologically from tests of endurance at the muscle level.
With respect to the latter, isokinetic dynamometry has the ability to isolate a group of
muscles about a specific joint under controlled conditions with stabilization of other joints, thus
providing a measure of muscle fatigue. It also provides a controlled, safe environment where no
resistance (load) is applied once the movement has ceased, since it accommodates to the amount
of muscle force that is applied (Jones & Stratton, 2000). Isokinetic muscle fatigue protocols for
the knee have been extensively developed in the healthy adult population. The most widely used
protocol consists of performance of a predetermined number of maximal repetitions, usually
between 25 and 50, at 180 degrees/second (Burdett & Van Swearingen, 1987; Pincivero, Gear,
& Sterner, 2001; Thorstensson & Karlsson, 1976). Another common protocol involves the
performance of consecutive repetitions until the peak torque or work decreases to 50% of the
maximum (Emery, Sitler, & Ryan, 1994). Calculation of a fatigue index (FI), which represents
the percentage decline in work or torque from the beginning to the end of the protocol, is the
most frequently reported parameter (Burdett & Van Swearingen, 1987; Pincivero et al., 2001;
Thorstensson & Karlsson, 1976), despite the fact that some have questioned its reliability
(Burdett & Van Swearingen, 1987). Alternatively, some authors have calculated the slope of the

13
regression line as a measurement of the decline in force and have found it to be more reliable
than the FI (Pincivero et al., 2001).
Existing isokinetic fatigue protocols have been modified for use with children (De Ste
Croix, Armstrong, & Welsman, 2003) and with other neurological populations, such as multiple
sclerosis (Lambert, Archer, & Evans, 2001). For example, slower testing speeds less than 100
degrees/second have been recommended for normally developing children due to difficulty
producing force at higher speeds (De Ste Croix et al., 2003; Gaul, 1996). Although no studies
were identified that have examined isokinetic muscle fatigue in individuals with CP, speeds of
30 (Van den Berg-Emons RJ, Van Baak, de, Speth, & Saris, 1996) and 90 (Ayalon, Ben-Sira,
Hutzler, & Gilad, 2000) degrees/second have been shown to be reliable in children with CP for
isokinetic strength assessment. In addition, isokinetic strength testing at 60 degrees/second has
been observed to be reliable in adults with CP (Holland, McCubbin, Nelson, & Steinman,
1994).
Reliable isokinetic fatigue protocols for the knee flexors and extensors have been
established for healthy children (De Ste Croix et al., 2003), adults (Emery et al., 1994;
Thorstensson & Karlsson., 1976), and those with various neurological impairments (Lambert et
al., 2001), with no studies found to date that have quantitatively assessed muscle fatigue via
isokinetic means in individuals with CP. Therefore, the primary purpose of this study was to
develop a feasible and reliable isokinetic fatigue protocol for use in CP, so that we could later
pose the question as to whether this aspect of muscle performance is impaired in this population.
The aim of the feasibility assessment was to determine if a group of mild to moderately impaired
subjects with CP of varying ages would be able to complete a muscle fatigue protocol. The aim
of the reliability assessment was to determine the repeatability of the fatigue parameters obtained
from the protocol. In order to evaluate the feasibility and reliability of these protocols, we

14
decided to study the knee flexors and extensors, since these are the most commonly studied

15
muscles in isokinetic protocols. In addition, we wanted to study more than one muscle group
because muscle characteristics may vary considerably across muscle groups, yielding different
results with respect to the determination of the presence or degree of muscle fatigability.
Methods
Subjects
Twelve subjects with a diagnosis of CP ranging in age from 10 to 22 years were recruited
for the feasibility assessment. Five of the 12 subjects were tested on two occasions, exactly one-
week apart at the same time of day, for the reliability analysis. All subjects were able to ambulate
at least short a distance with or without assistance and thus fell within Gross Motor Function
Classification System (GMFCS) levels I, II, and III (Table 2.1). Subjects were excluded if they
underwent orthopedic surgery within 9 months prior to the testing, received Botulinum toxin
injections to the quadriceps or hamstrings within 6 months prior to the testing, or suffered from
knee pain. Passive range of motion of the knee was also assessed prior to testing to determine if
the subject had sufficient range of motion to complete the test.
The protocol was approved by the Institutional Review Board at our institution. Written
permission from each participant over 18 years of age was obtained before beginning this study.
Participants under 18 years of age were required to have a parental permission form signed by
one parent or legal guardian. In addition, the minor was required to read and sign a child assent
form.
Procedures
An isokinetic dynamometer (Biodex Medical Systems Incorporated, Shirley, NY, USA)
was used to evaluate muscle fatigue and ‘strength’ by means of peak voluntary torque of the
knee flexors and extensors. Following familiarization with the isokinetic equipment and
explanation of procedures, the subject was positioned in the Biodex chair in a semireclining

16
sitting position with the angle of the hip joint at 70 degrees. The more involved lower extremity
was tested for subjects with bilateral involvement if they had sufficient motion and mobility in
that limb to perform the test. The involved lower extremity was tested for subjects with
unilateral involvement. The subject’s knee joint center was aligned with the center of rotation of
the isokinetic device. The leg was secured against the knee attachment pad and additional
stabilizing straps around the waist, the trunk, and over the mid-thigh portion were used to
restrain trunk and hip movement during testing. Following set-up, the passive range of motion
designated as “comfortable” by the patient, given the restrictions imposed by the chair which
limits flexion, was determined and used to set the limits of motion for the rest of testing session.
Subjects were instructed to keep their arms folded across their chest for all trials.
Table 2.1
Subject Characteristics and Feasibility Data
Subject Age, yr Gender GMFCS KE KF Reason for
level 50% rep 50% rep termination of test
1 10.3* M I 27 16 +
2 11.2 M I 24 self @ 35reps
3 11.4 F I 15 self @ 35reps
4 13.1 M II 100 reps
5 13.3* F I 26 26 +
6 14.4 F III 30 † @ 50reps
7 17.2 F I 30 21 +
8 19.9 F I 30 100 reps
9 20.6 F II 43 30 +
10 20.8* F II 32 self @ 35reps
11 22.5* F II 23 14 +
12 23.3* M III 73 55 +
KE50% rep = repetition where criteria for 50% decline were met for knee extension; KF50% rep
= repetition where criteria for 50% decline were met for knee flexion; self = self-termination
* = subjects tested twice, 1-week apart
+ = Goal of 35 repetitions and 50% decline in maximum peak torque achieved
† = unable to complete range of motion and reach target velocity
Subjects performed 8-12 submaximal concentric, reciprocal knee flexion and extension
repetitions to familiarize themselves with the procedure. After a 2 minute rest period, subjects

17
then performed 3 maximal concentric exertions for each muscle group at 60 degrees per second.
Strength was measured as the peak voluntary torque of each muscle group. Subjects were
instructed to “push” and “pull” their leg against the lever of the Biodex as hard and fast as
possible. Verbal encouragement was given for each repetition. One minute of rest was given
between repetitions and five minutes of rest was given prior to the muscle fatigue protocol to
prevent the occurrence of muscle fatigue.
During the protocol development phase prior to this study, it was determined that 60
degrees/second was the most comfortable speed for the majority of subjects. Therefore, the
fatigue protocol consisted of reciprocal, maximal concentric knee extension and flexion at 60
degrees/second until at least 35 repetitions were performed and peak torque declined to 50% of
maximum. This point was defined when the peak torque of 2-3 consecutive repetitions fell below
50% of the maximum torque value obtained during the fatigue protocol. A maximum of 100
repetitions was allowed to achieve the 50% decline in peak torque. In this manner, two isokinetic
testing protocols (35 repetitions and 50% decline) were imbedded within one session. Again, the
subjects were instructed to “push” and “pull” their leg against the lever as hard as possible.
Strong verbal encouragement was given for every repetition to encourage maximal effort on all
repetitions. The test was terminated if the subject could no longer move through their available
ROM at the desired velocity of 60 degrees/second or if self-terminated.
Data Analysis
Feasibility
During the fatigue protocol, the repetition in which the maximum torque occurred, as
well as the repetition in which the criteria for the 50% decline in peak torque were met, was
recorded. In addition, paired t-tests were used to test the difference between peak torques
obtained during the strength assessment versus the fatigue test.

18
Test-Retest Reliability
Data were gravity corrected, and only the constant velocity portion was used. Two
accepted measures of fatigue were computed for each of the two embedded protocols: 1) percent
decline in peak torque, calculated as a Fatigue Index (FI) (Pincivero, Gandaio, & Ito, 2003):
FI 100
PT last 5 reps x 100%
PT highest 5 reps
and 2) rate of decline in PT represented by the slope of the linear regression, beginning with the
first value of the highest 5 consecutive repetitions and ending with the last repetition (Pincivero
et al., 2001). The slope was also normalized by peak torque as a method for comparison across
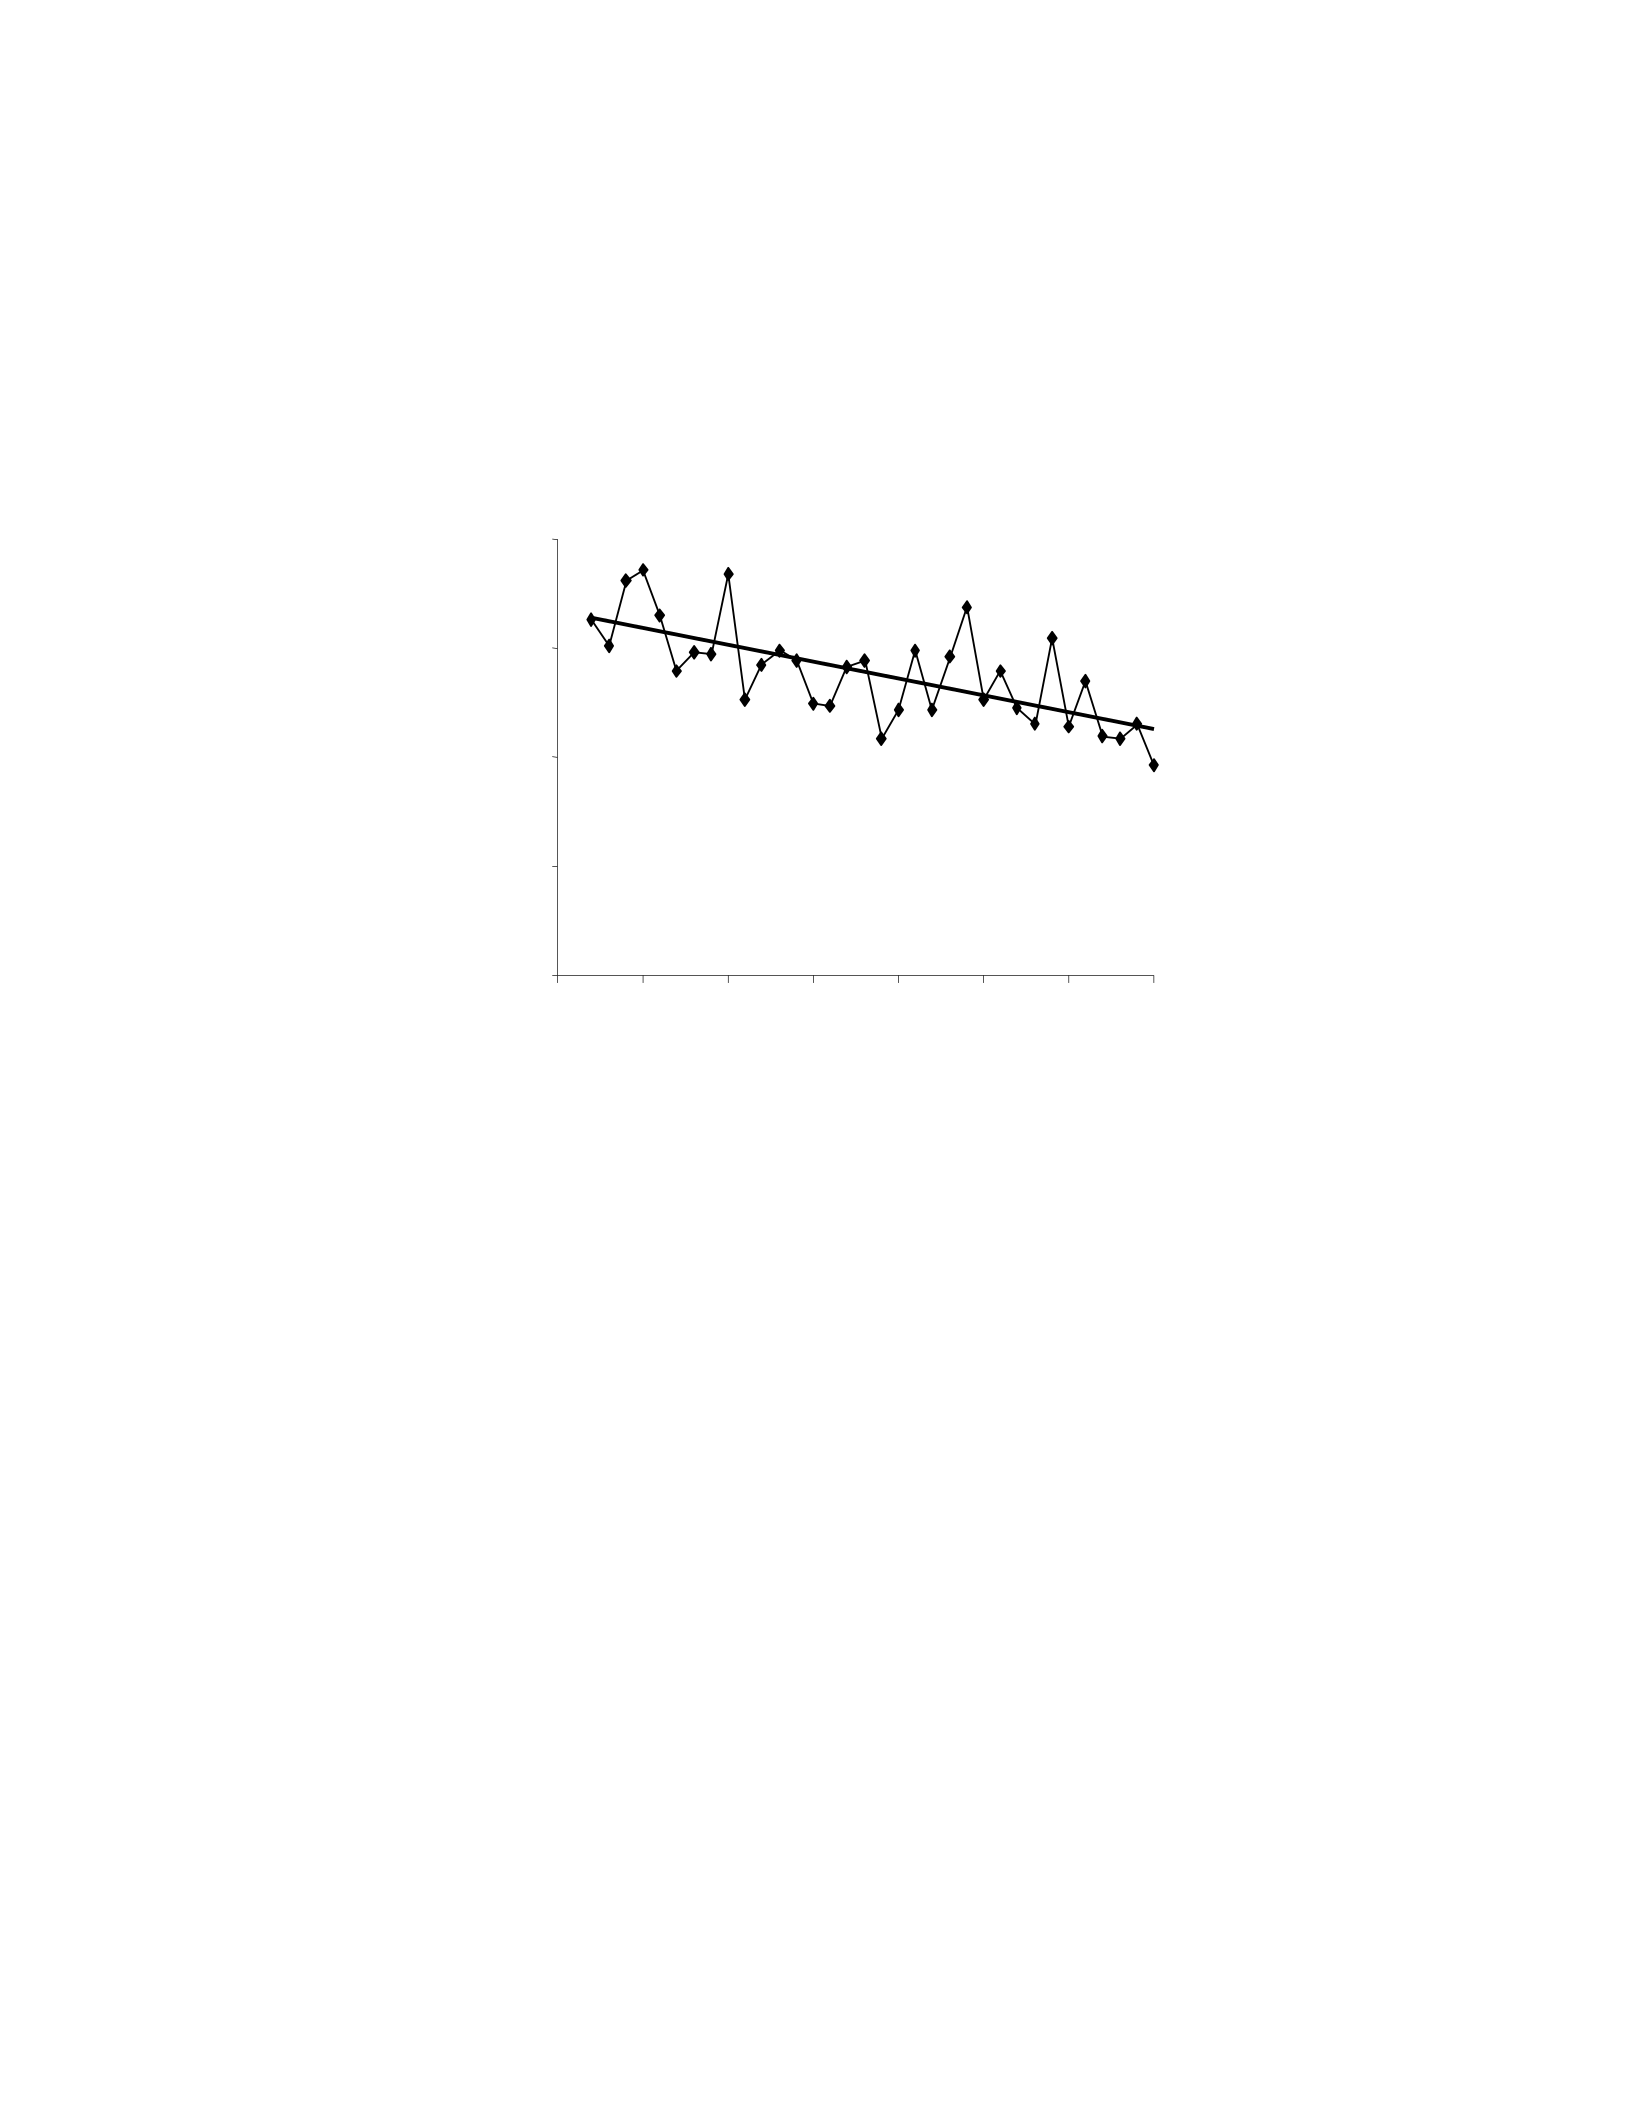
individuals (Felicetti, Zelaschi, & Di Patrizi, 1994) (Figure 2.1). Intraclass correlation
coefficients (ICC) were calculated to determine test-retest reliability for the slope, normalized
slope, and FI (Portney & Watkins, 2000). Alpha level was set at .05.
BMS EMS
(Shrout &Fleiss model from Portney & Watkins, 2000) ICC
BMS
where BMS is the between-subjects mean square, and EMS is the error mean square.
Results
Feasibility
In half of the 12 subjects tested, peak torque failed to decline to 50% of maximum in
either one or both directions during the fatigue protocol (Table 1). However, all subjects were
able to complete 35 repetitions. Furthermore, when the criteria for the 50% decline in peak
torque were met, it occurred before the 35th repetition in 82% of the trials. Reasons for
termination of the fatigue testing session are listed in Table 2.1 for each subject. Peak torque
obtained from the fatigue test for the knee extensors (55.6 ± 20.8) was significantly greater than
the value obtained during the single repetition strength assessment (42.7 ± 15.7, p = 0.001).
80
60
40
y = 0.6167x + 66.872
20 FI = 33.3%
0
0 5 10 1520253035
80
60
40
y = 0.6167x + 66.872
20 FI = 33.3%
0
0 5 10 15 20 25 30 35
19
However, there was no difference in peak torque for the knee flexors observed during the fatigue
test (24.6 ± 12.7) versus the strength test (22.5 ± 14.8, p = 0.18). It was noted that the maximum
torque during the fatigue test occurred between the 3rd and 27th repetition for the knee extensors
(9.3 ± 7.8) and between the 1st and 20th repetition for the knee flexors (5.0 ± 6.5).
Repetitions
Figure 2.1. Exemplar peak torque data during knee extension (PTKE) over 35 repetitions from
one subject represented by the diamond marker (). Slope of the linear regression and the
fatigue index (FI) were calculated and presented with the raw data.
Test-Retest Reliability
Because the 50% decline in peak torque did not occur in all subjects, fatigue
parameters were calculated only for the 35 repetitions. In one subject, the starting value, or the
first of the highest 5 consecutive repetitions, occurred later than the 15th repetition consistently
for both muscle groups during both test sessions. As a result, the protocol was extended to
achieve a sufficient number of repetitions beyond that point.
The ICC values of the absolute slope for the knee flexors and extensors were 0.94 and
0.97, while the ICC values of the normalized slope for the knee flexors and extensors were 0.83
PTKE (N-m)
20
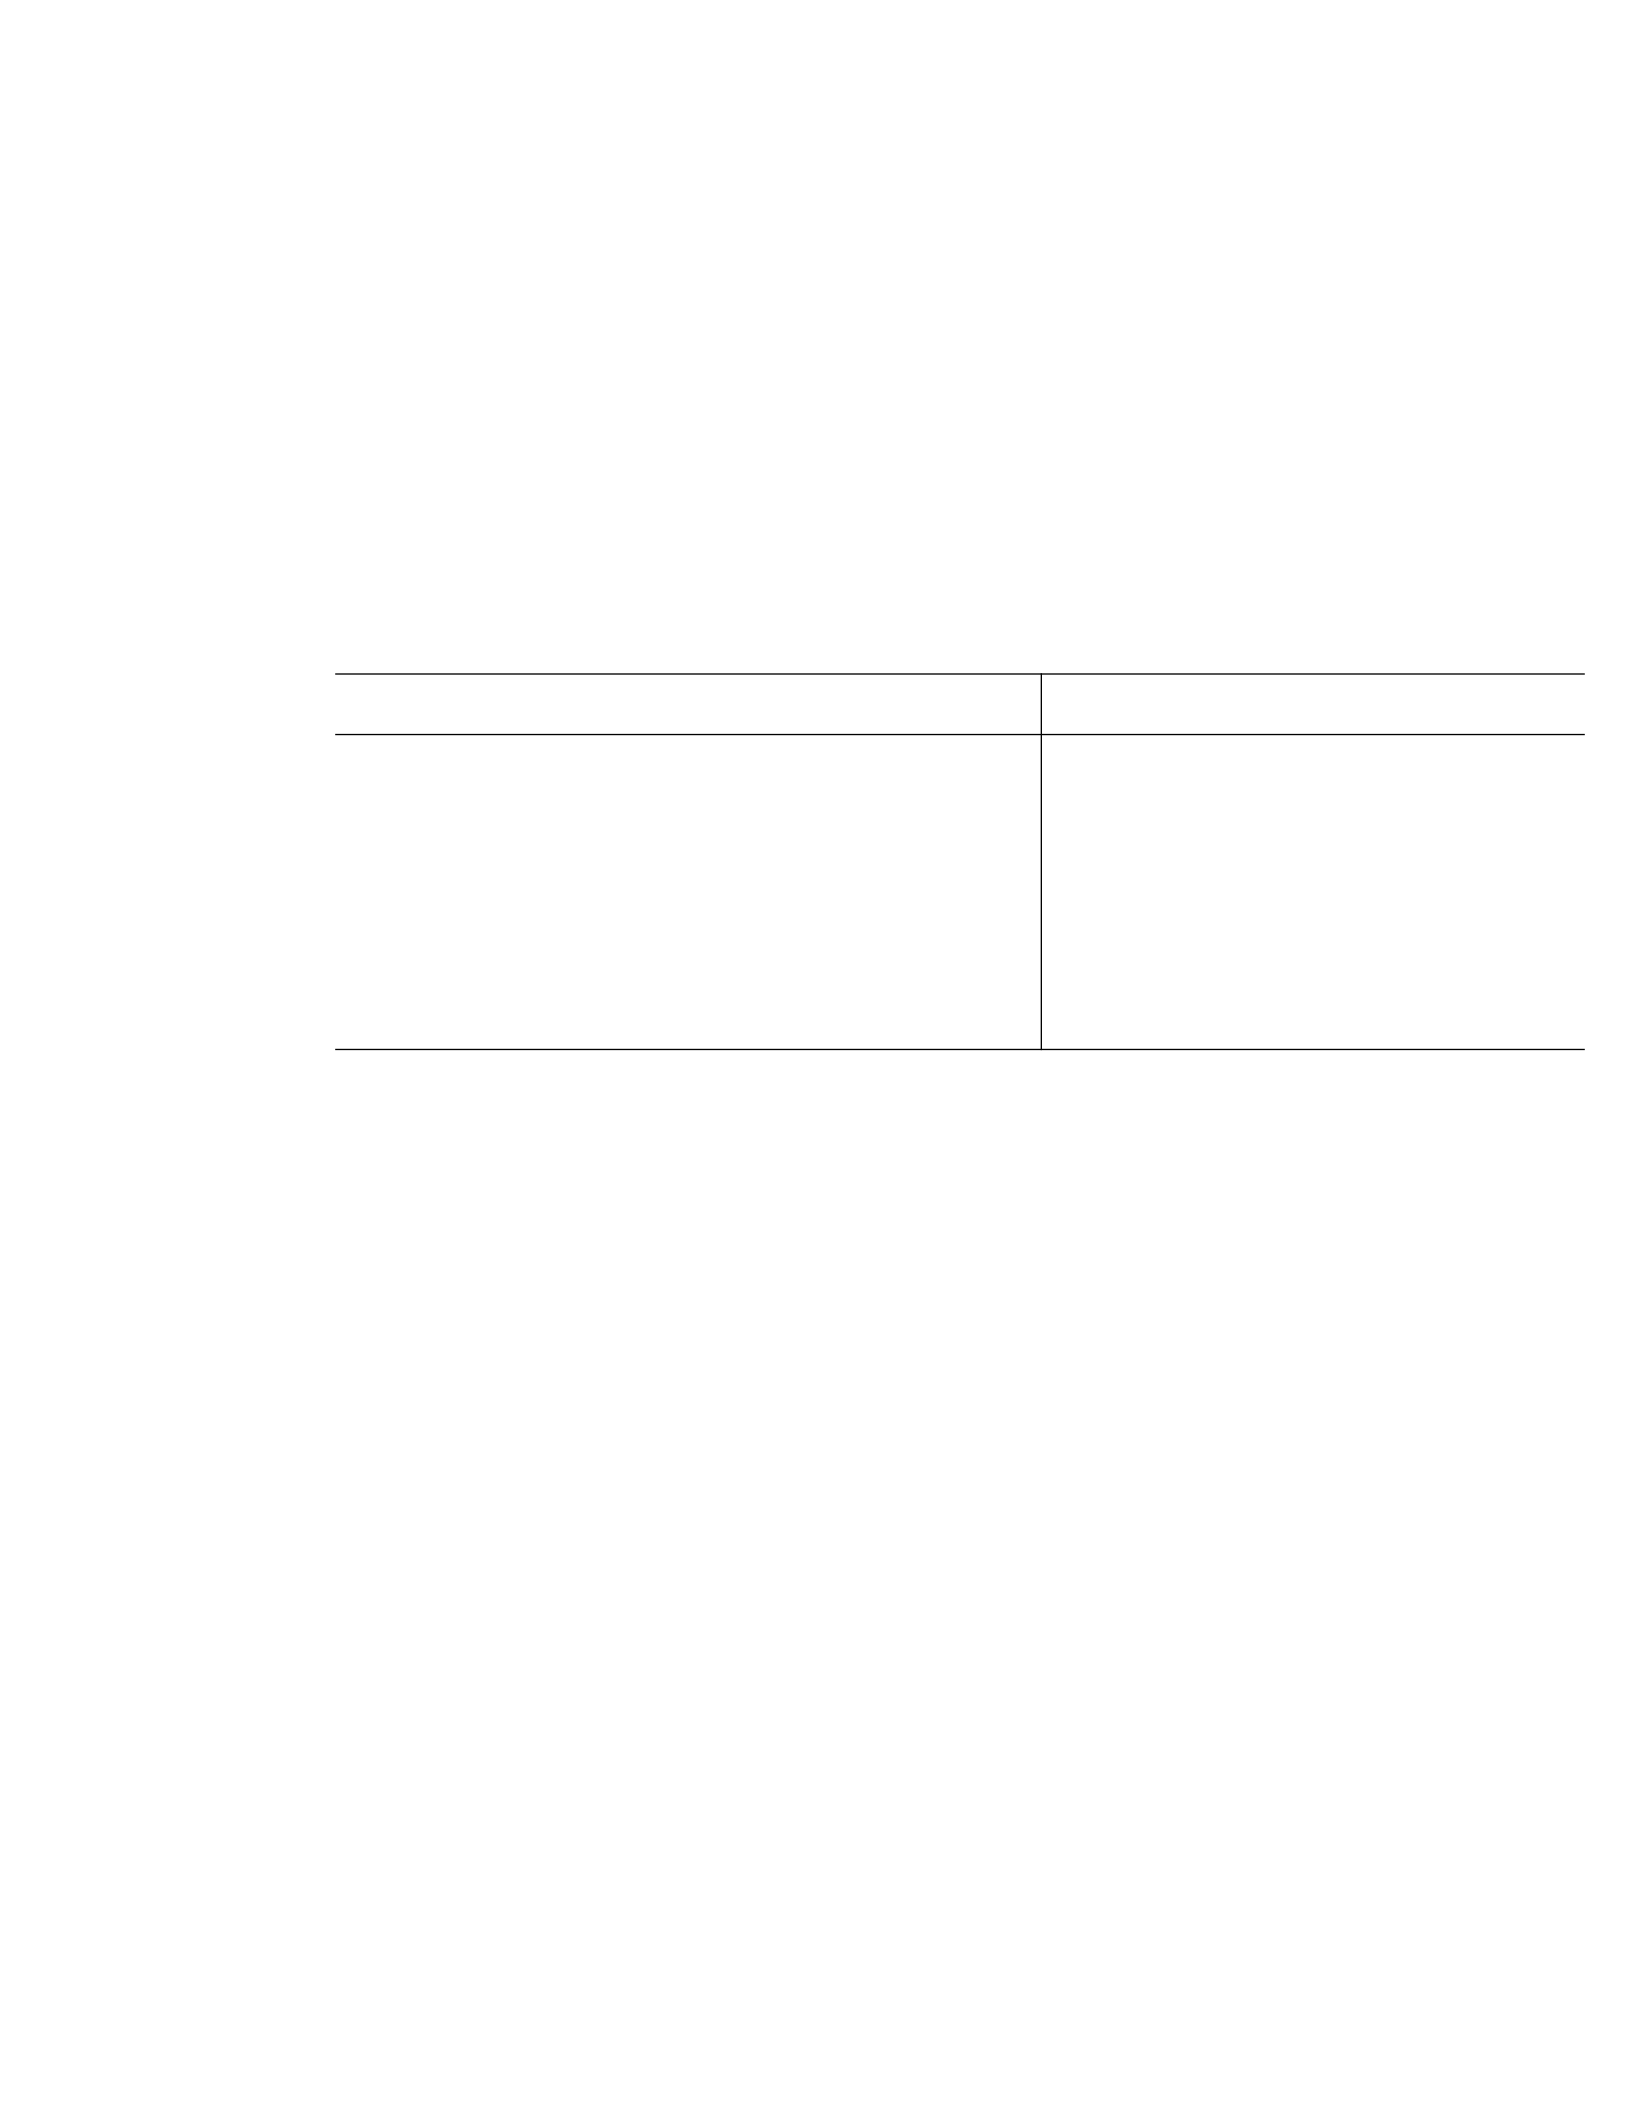
and 0.99, respectively. The ICC values of the FI were 0.86 and 0.73 for the knee flexors and
extensors, respectively. The ICC values of the peak torque from the strength test were 0.96 and
0.95, and the ICC values of the peak torque from the fatigue test were 0.89 and 0.87 for the
flexors and extensors, respectively (Table 2.2).
Table 2.2
Intraclass Correlation Coefficients (ICC) for Test-retest Reliability Analysis Knee Extension
Knee Flexion
Peak torque (PT) given in N-m. All the ICC values were significant at p < 0.05
FI = Fatigue Index; (Abs) = absolute value; Slope/PT = slope normalized by peak torque;
StrengthPT = peak torque calculated from strength test; FatiguePT = peak torque calculated from
fatigue test
Discussion
The results of this study demonstrate that muscle fatigue of the knee flexors and
extensors can be feasibly and reliably assessed in children and young adults with mild to
moderate CP over 35 repetitions at an isokinetic speed of 60 degrees/second. According to
Portney and Watkins (2000), ICC coefficients from .050 to 0.75 designate moderate reliability,
and values above 0.75 indicate good reliability. In addition, Shrout and Fleiss (Shrout & Fleiss,
1979) define ICCs exceeding 0.75 as excellent. Based on these guidelines, both the absolute and
normalized slope was observed to have good/excellent reliability for both the knee flexors and
extensors, whereas the FI presented with good/excellent reliability for the knee flexors only.
Moderate reliability (0.73) was observed for the FI of the knee extensors.
Test 1 Test 2 ICC Test 1 Test 2 ICC
FI 22.36 (14.89) 32.77 (8.57) .73 42.44 (11.59) 50.92 (14.95) .86
Slope
(Abs) 0.613 (0.380) 0.479 (0.298) .97 0.198 (0.121) 0.246 (0.156) .94
Slope/PT 0.013 (0.008) 0.010 (0.007) .99 0.012 (0.008) 0.011 (0.008) .83
StrengthPT 39.24 (20.42) 37.42 (16.32) .95 18.18 (14.57) 18.21 (13.63) .96
FatiguePT 49.54 (17.05) 49.48 (10.96) .87 18.21 (12.13) 22.09 (9.10) .89

21
The 50% decline protocol was not appropriate for use in this sample of individuals with
mild to moderate CP since only half of the subjects tested were able to achieve a 50% decline in
peak torque with the imposed limitations of 100 repetitions, self-termination, or inability to
complete the task. However, if the rate of decline is linear, it is possible that based on the slope,
this point could be extrapolated. When the 50% decline in peak torque was met, it occurred prior
to the 35th repetition in over 80% of the trials. Therefore, the protocol that required 35 repetitions
was more feasible for most subjects. However, in some subjects, the protocol may need to be
extended when the maximum torque occurs past the 15th repetition, as less than 20 repetitions
was not adequate in capturing the decline in torque in this sample of subjects. Testing at speeds
other than 60 degrees/second may produce different results than observed in this study. It is
possible that fewer repetitions could have been completed at 30 degrees/second. Since CP
encompasses such a wide range of motor disabilities, and subjects in this study tended to fall on
the milder end of the spectrum, these protocols may be increasingly problematic for individuals
with greater involvement (GMFCS levels IV and V) and may require further modification. It is
anticipated that reliable assessment of fatigue in those with greater involvement may not even be
possible.
Although the FI has been questioned in terms of its reliability (Burdett & Van
Swearingen, 1987), our results indicate that the FI has moderate to good reliability in the CP
population. Our results are comparable with other studies that have showed moderate to good
reliability of the FI for the non-dominant knee flexors and extensors (ICC = 0.84 and 0.74) in
the healthy adult population (Pincivero, Lephart, & Karunakara, 1997). The good/excellent
reliability of the slope calculations is also comparable to other studies in the healthy adult
population for the same muscle groups (ICC = 0.78 to 0.86) (Felicetti et al., 1994; Pincivero et
al., 2001).

22
Assessment of peak voluntary torque at 60 degrees/second as a measure of strength
presented with good/excellent reliability, with ICC values of 0.96 and 0.95 for the knee flexors
and extensors, respectively. Very little information is available in the literature regarding the
reliability of isokinetic testing speeds in CP. Based on Van den Berg-Emons et al. (1996)
reliability study, clinicians and researchers have considered the isokinetic speed of 30
degrees/second as the “gold standard” for strength assessment for people with CP. However,
faster angular velocities are more typical of everyday activities and movement. Furthermore,
recent research suggests that a faster speed of 90 degrees/second is also reliable for children and
adolescents with mild to moderate CP for the knee flexors and extensors (ICC = 0.98) (Ayalon et
al., 2000). Holland et al. (1994) also tested 14 adults (ages 17 to 38) at 60 degrees/second and
reported generalizability coefficients (ρ2) of 0.91 and 0.80 for the flexors and extensors,
respectively. The results of this study are comparable and provide further evidence to support the
reliability of speeds greater than 30 degrees/second for isokinetic strength assessments.
It is of clinical importance that peak torque was observed to be greater for the knee
extensors during the fatigue test as compared to the strength test. In non-disabled, healthy adults
and children, maximum torque is achieved during the first 5 repetitions (Burdett & Van
Swearingen, 1987; De Ste Croix et al., 2003; Pincivero et al., 2001; Pincivero et al., 1997).
Therefore, it is customary to utilize 3 to 5 isokinetic repetitions for maximum strength
assessments even in individuals with chronic motor disorders, such as CP (Ayalon et al., 2000;
Damiano & Abel, 1998; Holland et al., 1994; Van den Berg-Emons RJ et al., 1996). However,
according to our study, not only was peak torque greater for the knee extensors during the fatigue
test, but it occurred on average during the 9th repetition. The results indicate that we may not be
giving our subjects enough repetitions to achieve maximum torque during strength assessments
and may, in fact, be under representing their strength. Another reason for this discrepancy may

23
be that the subjects initiated knee extension during the strength test from a static position,
followed by knee flexion motion and a rest period before the next trial. Although the fatigue test
is initiated in this same manner, repetitions are performed consecutively without rest or pause,
where knee extension is not initiated from a static position on subsequent repetitions. Hence,
knee extension is preceded by a pre-stretch of the muscle (active knee flexion) during
subsequent trials, which may have a potentiation effect on the contractile machinery of the
quadriceps. This same phenomenon has been observed in stroke subjects during stretch-
shortening cycles compared to contractions from a static starting position (Svantesson, Grimby,
& Thomee, 1994). Knee flexion, on the other hand, begins from a dynamic position of pre-
stretch on all trials for both the strength and fatigue test, which may explain why a discrepancy
did not exist. However, further research is needed in order to decipher the influence of dynamic
versus contractions from a static position. Still other explanations, such as decreased neural
activation, need to be explored, because the production of the maximal torque after more than a
few repetitions is quite a deviation from normal muscle performance and may suggest that the
effort cannot possibly be maximal in those cases.
In conclusion, performance of 35 repetitions at 60 degrees/second is a feasible and
reliable isokinetic muscle fatigue protocol for both children and young adults with mild to
moderate CP and has widespread clinical and research applications. In addition, the number of
repetitions given and the type of contraction (dynamic/pre-stretch vs. static) may influence the
assessment of peak voluntary torque in subjects with CP.
Reference List
Ayalon, M., Ben-Sira, D., Hutzler, Y., & Gilad, T. (2000). Reliability of isokinetic strength
measurements of the knee in children with cerebral palsy. Dev.Med.Child Neurol., 42,
398-402.

24
Bigland-Ritchie, B., Johansson, R., Lippold, O. C., & Woods, J. J. (1983). Contractile speed and
EMG changes during fatigue of sustained maximal voluntary contractions.
J.Neurophysiol., 50, 313-324.
Burdett, R. G. & Van Swearingen, J. (1987). Reliability of isokinetic muscle endurance tests.
The Journal of Orthopaedic and Sports Physical Therapy, 8, 484-488.
Damiano, D. L. & Abel, M. F. (1998). Functional outcomes of strength training in spastic
cerebral palsy. Arch.Phys.Med.Rehabil., 79, 119-125.
Damiano, D. L., Martellotta, T. L., Sullivan, D. J., Granata, K. P., & Abel, M. F. (2000). Muscle
force production and functional performance in spastic cerebral palsy: relationship of
cocontraction. Arch.Phys.Med.Rehabil., 81, 895-900.
De Ste Croix, M. B. A., Armstrong, N., & Welsman, J. R. (2003). The reliability of an isokinetic
knee muscle endurance test in young children. Pediatric Exercise Science, 15, 313-323.
Emery, L., Sitler, M., & Ryan, J. (1994). Mode of action and angular velocity fatigue response of
the hamstrings and quadriceps. Isokinetics and Exercise Science, 4, 91-95.
Felicetti, G., Zelaschi, F., & Di Patrizi, S. (1994). Endurance tests during isokinetic contractions:
reliability of functional parameters. Isokinetics and Exercise Science, 4, 76-80.
Gaul, C. A. (1996). Muscular strength and endurance. In D.Docherty (Ed.), Measurement in
pediatric exercise science (pp. 225-254). Champaign, IL: Human Kinetics.
Holland, L., McCubbin, J., Nelson, E., & Steinman, S. (1994). Reliability of concentric and
eccentric muscle testing of adults with cerebral palsy. Adapted Physical Activity
Quarterly, 11, 261-274.
Hosking, J. P., Bhat, U. S., Dubowitz, V., & Edwards, R. H. (1976). Measurements of muscle
strength and performance in children with normal and diseased muscle. Arch.Dis.Child,
51, 957-963.
Jahnsen, R., Villien, L., Egeland, T., Stanghelle, J. K., & Holm, I. (2004). Locomotion skills in
adults with cerebral palsy. Clin.Rehabil., 18, 309-316.
Jones & Stratton, G. (2000). Muscle function assessment in children. Acta Paediatr., 89, 753-
761.
Lambert, C. P., Archer, R. L., & Evans, W. J. (2001). Muscle strength and fatigue during
isokinetic exercise in individuals with multiple sclerosis. Med.Sci.Sports Exerc., 33,
1613-1619.
Lundberg, A. (1976). Oxygen consumption in relation to work load in students with cerebral
palsy. J.Appl.Physiol, 40, 873-875.
Lundberg, A. (1978). Maximal aerobic capacity of young people with spastic cerebral palsy.
Dev.Med.Child Neurol., 20, 205-210.

25
MacPhail, H. E. & Kramer, J. F. (1995). Effect of isokinetic strength-training on functional
ability and walking efficiency in adolescents with cerebral palsy. Dev.Med.Child Neurol.,
37, 763-775.
Parker, D. F., Carriere, L., Hebestreit, H., & Bar-Or, O. (1992). Anaerobic endurance and peak
muscle power in children with spastic cerebral palsy. Am.J.Dis.Child, 146, 1069-1073.
Pincivero, D. M., Gandaio, C. M., & Ito, Y. (2003). Gender-specific knee extensor torque, flexor
torque, and muscle fatigue responses during maximal effort contractions.
Eur.J.Appl.Physiol, 89, 134-141.
Pincivero, D. M., Gear, W. S., & Sterner, R. L. (2001). Assessment of the reliability of high-
intensity quadriceps femoris muscle fatigue. Med.Sci.Sports Exerc., 33, 334-338.
Pincivero, D. M., Lephart, S. M., & Karunakara, R. A. (1997). Reliability and precision of
isokinetic strength and muscular endurance for the quadriceps and hamstrings.
Int.J.Sports Med., 18, 113-117.
Portney, L. G. & Watkins, M. P. (2000). Foundations of clinical research: Applications to
practice. (2nd ed.) Upper Saddle River, NJ: Prentice-Hall.
Rose, J., Haskell, W. L., & Gamble, J. G. (1993). A comparison of oxygen pulse and respiratory
exchange ratio in cerebral palsied and nondisabled children. Arch.Phys.Med.Rehabil., 74,
702-705.
Shrout, P. A. F. & Fleiss, J. L. (1979). Intraclass correlation: uses in assessing rater reliability.
Psychol Bull, 85, 420-428.
Svantesson, U., Grimby, G., & Thomee, R. (1994). Potentiation of concentric plantar flexion
torque following eccentric and isometric muscle actions. Acta Physiol Scand., 152, 287-
293.
Thorstensson, A. & Karlsson, J. (1976). Fatiguability and fibre composition of human skeletal
muscle. Acta Physiol Scand., 98, 318-322.
Van den Berg-Emons RJ, Van Baak, M. A., de, B., Speth, L., & Saris, W. H. (1996). Reliability
of tests to determine peak aerobic power, anaerobic power and isokinetic muscle strength
in children with spastic cerebral palsy. Dev.Med.Child Neurol., 38, 1117-1125.

26
CHAPTER 3: ARE MUSCLES MORE FATIGABLE IN INDIVIDUALS WITH CEREBRAL
PALSY?
Introduction
Measures of physiological capacity, such as lower extremity muscle strength, have been
correlated with functional measures in people with cerebral palsy (CP) and other disabilities
(Damiano & Abel, 1998; Damiano, Kelly, & Vaughn, 1995; Kramer & MacPhail, 1994).
However, neither muscle strength nor measures of physical function have been shown to be
related to psychosocial aspects of quality of life (QOL), such as comfort and happiness (Pirpiris
et al., 2006). Self-reported physical fatigue, on the other hand, has been significantly associated
with QOL measures of psychosocial well-being, such as bodily pain, limitations in physical and
emotion role function, and low life satisfaction in adults with CP (Jahnsen, Villien, Stanghelle,
& Holm, 2003). Furthermore, adults with CP report fatigue as a main cause of the deterioration
or cessation of their walking ability (Bottos, Feliciangeli, Sciuto, Gericke, & Vianello, 2001;
Jahnsen, Villien, Egeland, Stanghelle, & Holm, 2004; Murphy, Molnar, & Lankasky, 1995).
However, these studies assessed fatigue using questionnaires and interviews and did not attempt
to differentiate among objective measures of fatigue.
There are different types of objective measures of fatigue, such as cardiorespiratory
fatigue (e.g. heart beating too fast or person feeling out of breath), neural or psychological
fatigue (increased sense of effort or feeling as if muscles are going to ‘give out’) or local muscle
fatigue. Muscle fatigue, or fatigability, was defined as a reduction in force output that occurs
during sustained activity (Bigland-Ritchie, Johansson, Lippold, & Woods, 1983). Fatigue
resistance is also referred to as muscle endurance, which is the term most often used in the
literature as the antonym, or opposite, of muscle fatigue, similar to the use of strength vs.
weakness.

27
Previous objective clinical measures of fatigue in people with CP were focused primarily
on the cardiorespiratory system. Although it has been well documented that children and
adolescents with CP have lower VO2max than their typically developing peers, most authors
agreed that local muscle factors, such as muscle fatigue, were responsible for the lower VO2max
and limitations in activity (Hoofwijk, Unnithan, & Bar-Or, 1995; Lundberg, 1978; Rose, Haskell,
& Gamble, 1993; Tobimatsu, Nakamura, Kusano, & Iwasaki, 1998; Unnithan, Dowling, Frost, &
Bar-Or, 1996). Following this same argument, Lundberg (1978) and Hoofwijk et al. (1995)
suggested that spastic muscles may have decreased venous return and inhibited muscle lactate
clearance during exercise, thereby increasing local muscle fatigue and leading to a decrease in
VO2max values.
Several investigators have studied muscle endurance from an anaerobic perspective in
children and adolescents with CP by means of the Wingate Anaerobic Cycling Test (WAnT).
The WAnT is a widely used, validated measure of anaerobic performance during which the
subject pedals at maximal speed against a predetermined constant resistance for 30 seconds
(Bar- Or, Dotan, & Inbar, 1977). Results from these studies indicate that mean muscle power, as
a measure of muscle endurance, is markedly deficient in people with CP (Parker, Carriere,
Hebestreit, & Bar-Or, 1992; Parker, Carriere, Hebestreit, Salsberg, & Bar-Or, 1993; Tirosh, Bar-
Or, & Rosenbaum, 1990). However, due to the focus on speed and the short duration of the test,
the validity of this test as a measure of muscle endurance is debatable. Also, it cannot
differentiate between right and left extremities nor can it differentiate among muscle groups.
Therefore, it is at best a non-specific, gross physiologic measurement of endurance or, perhaps
more appropriately, of muscle power.
Because muscles adapt to the amount and type of neural stimulation being imposed upon
them, secondary effects of spasticity on muscle tissue can also have a profound impact on the

28
ability to generate and maintain muscle force. Muscle abnormalities such as alterations in muscle
fiber size and fiber type distribution, excessive collagen accumulation, and increased stiffness of
spastic muscle cells have been extensively reported (Booth, Cortina-Borja, & Theologis, 2001;
Castle, Reyman, & Schneider, 1979; Friden & Lieber, 2003; Ito et al., 1996; Marbini et al.,
2002; Romanini, Villani, Meloni, & Calvisi, 1989; Rose et al., 1994). These alterations of
muscle properties can have major implications for essential aspects of muscle performance, such
as the ability to generate force and to sustain force output. In cerebral palsy and other motor
disorders, different muscle groups can be affected to varying degrees; therefore, these changes
may also be muscle-specific.
Isokinetic muscle fatigue protocols for the knee have been extensively developed in the
healthy adult population. (Burdett & Van Swearingen, 1987; Pincivero, Gear, & Sterner, 2001;
Thorstensson & Karlsson, 1976) and have been modified for use with children (De Ste Croix,
Armstrong, & Welsman, 2003) and with other neurological populations, such as multiple
sclerosis (Lambert, Archer, & Evans, 2001). Isokinetic dynamometry has the ability to isolate a
group of muscles about a specific joint under controlled conditions with stabilization of other
joints, thus providing a device with which to measure muscle fatigue. It also provides a
controlled, safe environment where no resistance (load) is applied once the movement has
ceased, since it accommodates to the amount of muscle force that is applied (Jones & Stratton,
2000). An isokinetic fatigue protocol was developed recently by our group for use in children
and young adults with mild to moderate CP and was shown to be feasible and reliable for testing
the knee flexors and extensors (Moreau, Li, & Damiano, 2006).
The primary purpose of this study was to determine whether muscle fatigue in the knee
flexors and extensors in individuals with CP differs from those without a motor disability. A
secondary purpose of the study was to determine the relationship of fatigue to functional level,

29
walking velocity, and psychosocial well-being and activity / participation as measured by the
Pediatric Outcomes Data Collection Instrument (PODCI). We hypothesized that individuals with
CP would have greater levels of muscle fatigability compared to non-disabled peers, and that this
aspect of muscle performance would be inversely related to functional level, walking velocity,
activity and participation, and psychosocial well-being.
Methods
Subjects
A group of 18 subjects with cerebral palsy (CP) and 16 control subjects without a motor
disability between the ages of 10 and 25 were recruited for the study. Gender and age
distribution was similar across groups. Physical demographics of the subjects are listed in Table
3.1. All subjects were able to ambulate at least a short distance with or without assistive devices.
Subjects were excluded if they had orthopedic surgery within 12 months prior to the testing,
received Botulinum toxin injections to the quadriceps or hamstrings within 6 months prior to
testing, or complained of existing knee pain. Passive range of motion of the knee was also
assessed prior to testing to determine if the subject had sufficient range of motion to complete
the test.
The study was approved by the Institutional Review Board at our institution. Written
informed consent from each participant over 18 years of age was obtained before beginning this
study. Participants younger than 18 years of age were required to have a parental consent form
signed by one parent or legal guardian. In addition, the minor was required to read and sign a
child assent form.
Gross Motor Function Classification System
All subjects were assigned a Gross Motor Function Classification System (GMFCS) level
and were restricted to levels I, II, and III, secondary to ambulation requirements of the study. The

30
GMFCS is a standardized evaluation that allows for the classification of children with CP into
levels based on functional ability. Emphasis is on the child's usual performance in home, school,
and community settings. The GMFCS has been suggested to have good to excellent interrater
reliability for severity of gross motor function limitations in children with CP (Palisano et al.,
1997; Wood & Rosenbaum, 2000). In addition, it has been shown to be a valid instrument in
both cross-sectional (Palisano et al., 1997) and longitudinal (Wood & Rosenbaum, 2000)
studies.
Table 3.1.
Physical Demographics
Gender Age range Age (yr) ± SD Height (m) ± SD Weight (kg) ± SD
CP 13F/5M 10 – 25 17.49 ± 5.03 1.52 ± 0.08 47.57 ± 9.92
Control 13F/3M 10 – 23 16.61 ± 4.45 1.59 ± 0.09* 53.97 ± 9.72
M = male; F = female. *The control group was significantly taller than the CP group (P = 0.01)
Pediatric Outcomes Data Collection Instrument (PODCI)
The Pediatric Outcomes Data Collection Instrument (PODCI) questionnaire was
completed separately by the parent and child or by the adult subject only (AAOS/POSNA,
Version 2.0, (Daltroy, Liang, Fossel, & Goldberg, 1998). The PODCI was designed to assess
self-reported physical function and psychosocial aspects of health status in children with mild to
moderate musculoskeletal disability. The PODCI contains 108 short questions and takes about
10-20 minutes to complete. Each scale is computed to generate a score from 0 to 100 (worst to
best). The following scales generated from this instrument were analyzed:
Transfer and Basic Mobility Scale: Measures difficulty experienced in performing routine
motion and motor activities in daily activities.
Sports/Physical Functioning Scale: Measures difficulty or limitations encountered in
participating in more active activities or sports.

31
Pain/Comfort Scale: Measures the level of pain experienced during the past week.
Global Functioning Scale: A general combined scale calculated from the first three
scales listed above and the ‘Upper Extremity and Physical Function Scale’.
Happiness Scale: Measures overall satisfaction with personal looks and sense of
similarity to friends and others of own age.
Satisfaction with Symptoms Scale: Measures the patient's acceptance of current
limitations should this be a life long state.
Gait Velocity
Gait velocity was assessed over level ground prior to isokinetic testing. A 10-m distance
was marked on the floor with tape. Subsequent marks were placed 2-m from the starting point
and 2-m from the ending point, thus allowing a 6-m timed middle section for the test. Timing
began when the subject crossed the initial 2-m mark and ended when the subject crossed the
final 2-m mark. Each subject was given 2-4 trials at a comfortable walking speed and at a fast
walking speed. The instructions for comfortable walking speed were, “When I say ‘go’, walk all
the way to the last piece of tape at your comfortable walking speed.” For the fast walking speed,
the instructions were, “When I say ‘go’, walk all the way to the last piece of tape as fast as
possible but without running”. Time was recorded by a stopwatch in seconds, and velocity was
calculated as meters per second. Two representative trials at each speed were averaged (Brusse,
Zimdars, Zalewski, & Steffen, 2005).
Isokinetic Testing
An isokinetic dynamometer (Biodex Medical Systems Incorporated, Shirley, NY, USA)
was used to record torque of the knee flexors and extensors during maximum voluntary
contraction throughout the available range of motion. Following familiarization with the
isokinetic equipment and explanation of procedures, the subject was positioned in the Biodex

32
chair in a semireclining sitting position with the angle of the hip joint at 70 degrees (thigh
horizontal and trunk 70 degrees above horizontal). The more involved lower extremity was
tested for subjects with bilateral or unilateral involvement if they had sufficient motion and
mobility in that limb to perform the test. The left lower extremity was tested for control subjects.
The subject’s knee joint center was aligned with the center of rotation of the dynamometer. The
leg was secured against the knee attachment pad, and additional stabilizing straps around the
waist, the trunk, and over the mid-thigh portion were used to restrain trunk and hip movement
during testing. Following set-up, the passive range of motion designated as “comfortable” by the
patient, given the restrictions imposed by the chair itself which limits flexion, was determined
and used to set the limits of motion for the rest of testing session. Subjects were instructed to
keep their arms folded across their chest for all trials.
Subjects performed 8-12 submaximal concentric, reciprocal knee flexion and extension
repetitions to familiarize themselves with the procedure. After a 2-minute rest period, subjects
then performed 3 maximal concentric exertions for each muscle group at 60 degrees per second.
Five minutes of rest was given prior to the muscle fatigue protocol to prevent the occurrence of
muscle fatigue.
The fatigue protocol consisted of reciprocal, maximal concentric knee extension and
flexion at 60 degrees/second for 35 repetitions. The subjects were instructed to “push” and “pull”
their leg against the lever as hard as possible. Strong verbal encouragement was given for every
repetition to encourage maximal effort on all repetitions (Moreau et al., 2006).
Data were gravity corrected, and only the constant velocity portion was used for the
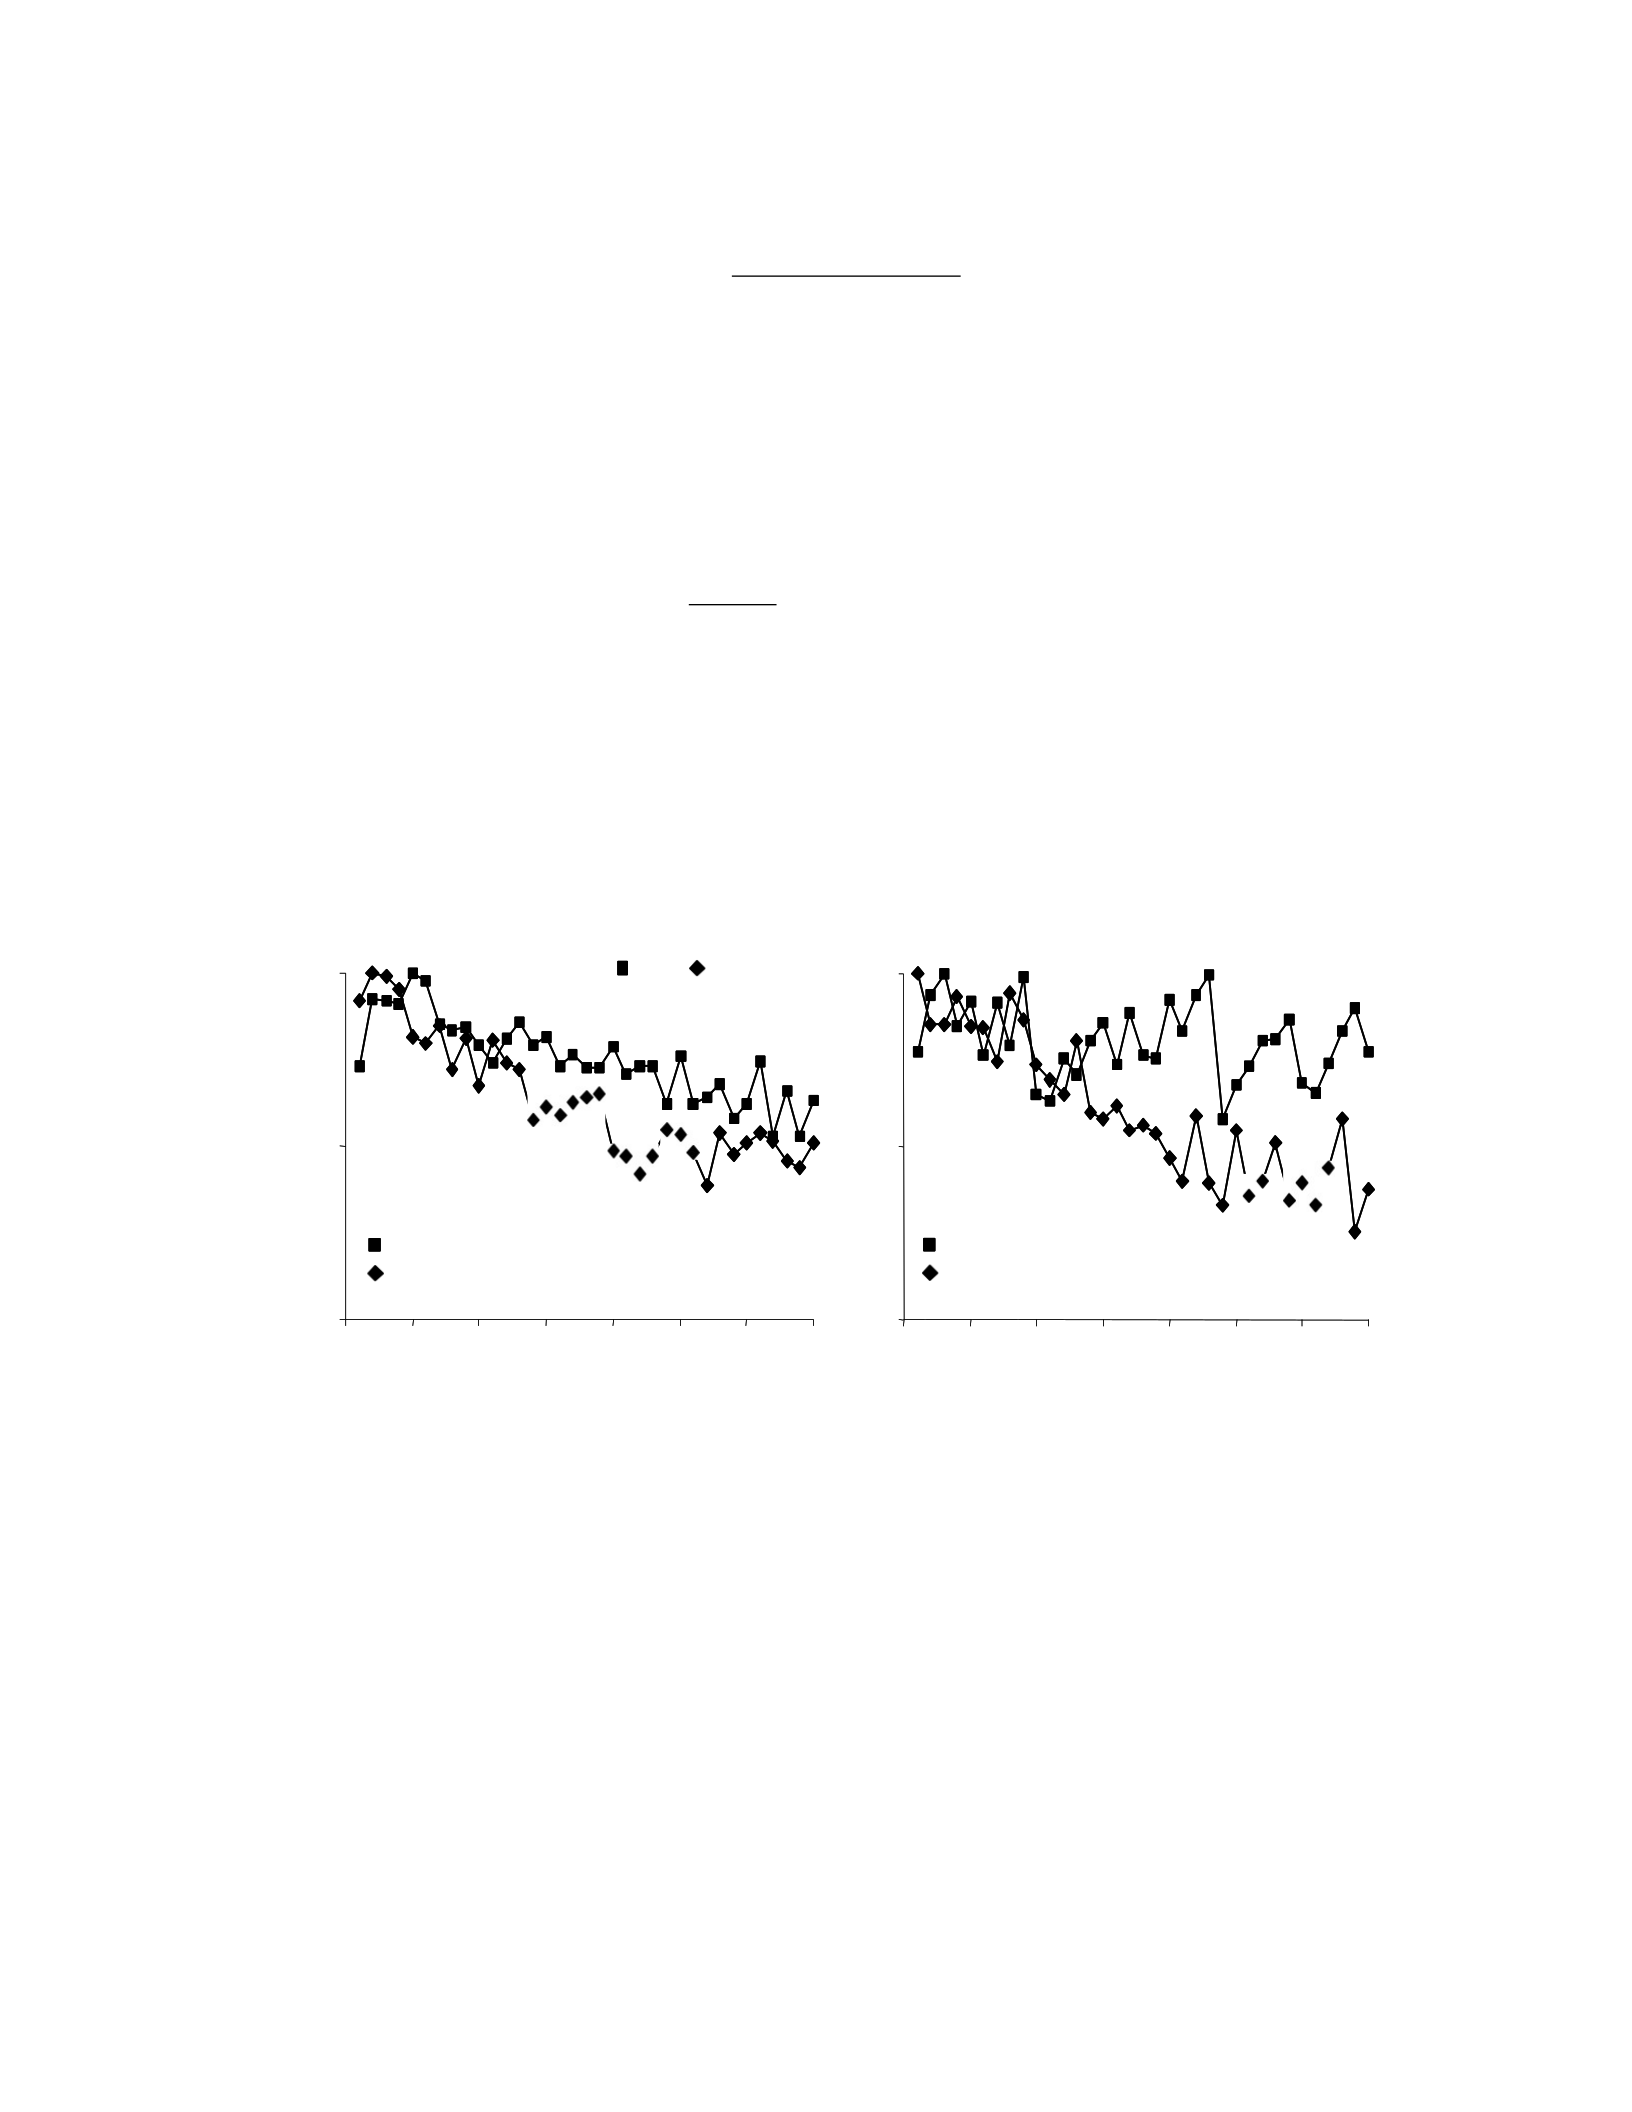
following calculations. Two accepted measures of fatigue were computed as illustrated in Figure
3.1: 1) percent decline in peak torque (PT), calculated as a Fatigue Index (FI) (Pincivero,
CPControl
FI = 33%; b = 0.62
FI = 54%; b = 2.59
33
Gandaio, & Ito, 2003): FI 100
PT last 5
reps
x 100%
PT highest 5 reps
and 2) rate of decline in PT represented by the slope of the linear regression, beginning with the
first value of the highest 5 consecutive repetitions and ending with the last repetition (Pincivero
PT
et al., 2001): Slope
∆Reps
This fatigue protocol was previously shown to be feasible and reliable in children and young
adults with mild to moderate CP (Moreau et al., 2006).
a.) b.)
1 1
0.5 0.5
0
0 5 10 15 20 25 30 35 0
0 5 10 15 20 25 30 35
Repetitions
Figure 3.1. Exemplar peak torque data during knee extension (PTKE) over 35 repetitions from
a.) one subject with CP classified as GMFCS level I and b.) one subject classified as GMFCS
level III. Two age-matched subjects from the Control group are illustrated for comparison. Slope
(b) of the linear regression and the fatigue index (FI) were calculated and presented with the raw
data. For illustrative purposes, PT was normalized by the maximum torque to yield a scale of 0
to 1.
Statistical Analysis
Factorial Repeated Measures Analysis of Variance (ANOVA) procedures, with muscle
(extensors/flexors) as the repeated measure, were used to test for differences in fatigue
FI = 19%; b = 0.07
FI = 56%; b = 2.26
Normalized PTKE

34
parameters between groups. Within the group with CP, Pearson correlation procedures were
used

35
to relate gait velocity and PODCI scores to fatigue parameters, and a Spearman rank procedure
was used for comparisons with the ordinal GMFCS categorization (levels I, II, and III).
ANOVA procedures were also used to compare fatigue parameters across GMFCS levels in the
subjects with CP. Alpha level was set at 0.05.
Results
The demographics of the two groups were similar with the control group slightly taller
than the group with CP (p = 0.01, Table 3.1). The peak absolute torque of the knee extensors
obtained during the fatigue protocol for the group with CP and the control group were 54.2 ±
20.8 and 108.4 ± 37.9 N-m, respectively. For the knee flexors, the peak absolute torque was 24.2
± 11.3 and 57.7 ± 21.3 N-m for the group with CP and the control group, respectively. The slope
of the knee extensors and flexors were significantly correlated with age only for the control
group (Control: r = 0.71 and 0.82, p < 0.05; CP: r = 0.002 and -0.12, respectively). Gender did
not have a significant effect on within group or between group comparisons for either the FI or
the slope. Therefore, gender was excluded as a factor in the ANOVA procedures.
Fatigue
PT occurred at the 22nd and 27th repetition during the fatigue protocol for knee extension
in 2 subjects. Therefore, the protocol was extended to 50 repetitions, so that a sufficient number
of data points were obtained to see a clear trend and to be able to make equal comparisons
across subjects. Figure 3.2 illustrates the mean and standard error of the mean (SEM) of the
slope for the knee flexors and extensors for both groups. Compared to the group with CP, the
control group was associated with greater slope values for both the knee flexors and extensors,
indicating greater fatigability of the control group (Group: F1,60 = 36.90, P < 0.0001). The knee
extensors were associated with greater slope values than the knee flexors across both groups
(Muscle: F1, 60 = 21.86, P < 0.0001). No significant group and muscle interaction was observed.
36
2
1
0 Extension Flexion
Figure 3.2. Mean and SEM of the slope for knee flexion and extension for the group with CP
and the control group. Significant differences were observed among the different groups (P <
0.0001) and different muscles (P < 0.0001). No significant interaction between Group and
Muscle was observed.
60
40
20
0Extension Flexion
Figure 3.3. Mean and SEM of the Fatigue Index (FI) for knee flexion and extension for the
group with CP and the control group. Significant differences were observed among the different
groups (P = 0.009) and different muscles (P = 0.004). No significant interaction between Group
and Muscle was observed.
CP
Control
CP
Control
Slope PT (N·m·rep-1)
FI (% decline in PT)
37
GMFCS
Greater slope values were associated with lower GMFCS levels in the group with CP,
regardless of muscle group (F2,27 = 5.25, P = 0.012).. Post-hoc analysis with Tukey adjustments
revealed significant differences between GMFCS levels I and III and between levels II and III (P
= 0.009 and 0.037, respectively). Figures 3.1a and 3.1b illustrate the FI and the slope of the
decline in knee extensor PT for a subject within GMFCS level I and level III, respectively. A
significant interaction between GMFCS and muscle group was not observed. Spearman rank
correlations revealed a significant negative association between GMFCS level and the slope for
knee extension only, as illustrated in Figure 3.4 (r = -0.47, P = 0.047). Thus, more proficient
ambulators with CP, i.e. lower GMFCS levels, had greater levels of knee extensor fatigability.
There were no significant main effects or interactions for the FI across GMFCS levels.
1.0
n=10
0.5 n=5
n=3
0.0
I II III
Figure 3.4. Spearman rank (r) correlation between the slope of the knee extensors (KE) and
GMFCS levels I, II, and III (r = -0.474, P = 0.047). Mean and SEM are illustrated.
PODCI
The Global Function scale of the PODCI was directly correlated with both the slope and
FI of the knee extensors, while the Sports and Physical Function scale was directly related to the
Slope KE (N·m·rep-1)

38
slope only. Transfers and basic mobility were directly correlated to the slope and FI of the knee
extensors, as well as to the slope of the knee flexors. A positive correlation indicates that people
with higher levels of functioning (i.e. higher scores on the PODCI) have increased levels of
fatigability. None of the scales related to psychosocial well-being (Pain/comfort, happiness,
satisfaction) were correlated with the fatigue parameters. Correlation coefficients are listed in
Table 3.2.
Velocity
Among the normalized and non-normalized self-selected and fast velocities, only non-
normalized fast velocity was significantly correlated to the slope of the knee extensors (r = 0.51,
P = 0.03). Therefore, the capacity to walk faster is associated with greater levels of knee extensor
fatigability among the subjects with CP.
Table 3.2
Pearson (r) correlations of PODCI subscales and velocity data with fatigue parameters
Physical Function
& Basic Mobility
Functioning
Scale
Comfort
Satisfaction
PODCI = Pediatric Outcomes Data Collection Instrument; Slope KE = slope of peak torque for
knee extension; Slope KF = slope of peak torque for knee flexion; FI = Fatigue Index
Slope KE Slope KF FI KE FI KF
PODCI Sports & 0.50* 0.40 0.40 0.23
PODCI Transfers 0.55* 0.49* 0.55* 0.37
PODCI Global 0.47* 0.30 0.50* 0.29
PODCI Happiness 0.34 0.43 0.23 -0.09
PODCI Pain & 0.01 0.02 -0.25 0.07
PODCI 0.10 0.13 -0.18 0.14

39
Discussion
Contrary to our hypotheses, the knee flexors and extensors in our sample of subjects with
CP were actually less fatigable than in the age-matched control group, as indicated by both Slope
and FI. Furthermore, higher levels of fatigability (Slope) were associated with higher functioning
GMFCS levels, higher levels of function as measured by the PODCI Transfers and Basic
Mobility scale and fast velocity, and greater levels of participation in sports and other activities
for the CP group. Counterintuitively, it appears as though lower levels of fatigability of the knee
flexors and extensors are characteristic of greater disability.
This fatigue protocol was designed as a measure of volitional activity, which would be
more representative of everyday function versus an electrically elicited fatigue test or an
isometric test. Nevertheless, our results are similar to a study that utilized an electrically elicited
fatigue test where the quadriceps were found to be less fatigable than a control group
(Stackhouse, Binder-Macleod, & Lee, 2005). However, it should be noted that voluntary
contractions, which form the basis of our study, were not part of the fatigue test. Because the
muscles were electrically stimulated, only peripheral aspects of muscle fatigue distal to the
peripheral motor nerve were assessed. Our study, on the other hand, encompassed both central
and peripheral aspects of muscle fatigue, from the central nervous system command to the
contractile apparatus of the muscle itself. Furthermore, electrically elicited fatigue tests differ
from volitional fatigue tests in the order of activation of muscle fibers, as well as in the firing
rate and synchrony of nerve depolarizations (Delitto & Snyder-Mackler, 1990). Therefore,
similarities between the two studies should be interpreted within this context.
Our results differ from anaerobic tests previously reported by Parker et al. (1992, 1993)
and Tirosh et al. (1990). Results from these studies indicate that peak muscle power and mean
power, as a measure of muscle endurance, are markedly deficient in people with CP (Parker et

40
al., 1992; Parker et al., 1993; Tirosh et al., 1990). However, these authors assessed muscle
endurance, or fatigue resistance, in subjects with CP by means of the Wingate Anaerobic Cycling
Test (WAnT). From this 30-second, maximal cycling test, mean power is calculated as a measure
of endurance. However, mean power is an absolute measure that reflects the average level of
explosiveness or power and does not reflect the decline in the force-generating capacity of the
muscle. Therefore, the differences in measurement parameters between our study and the
aforementioned explain the discrepancy in results.
Several mechanisms can be suggested to explain the greater fatigue resistance of the CP
group, the first of which are maximal torque level (strength) and muscle mass. It has been
suggested that males are more fatigable than females (Hunter & Enoka, 2001; Pincivero et al.,
2003), and adults are more fatigable than children (Kanehisa, Okuyama, Ikegawa, & Fukunaga,
1995) and older adults (Lanza, Russ, & Kent-Braun, 2004) due to greater strength and/or greater
muscle mass. The muscle mass or strength hypothesis states that stronger subjects would have
more blood flow occlusion than weaker subjects at the same relative load, particularly during
isometric tasks (Barnes, 1980). While gender was not predictive of muscle fatigue in our sample
of subjects with CP, the peak absolute torque of both muscle groups obtained during the fatigue
test was 50% lower in the CP group compared to the control group and could partially explain
the greater fatigue resistance. Perhaps, the lower capacity for force production in the subjects
with CP prohibits the rapid decline in torque that was observed in the control group. However, it
should be noted that gender and age differences in fatigability due to absolute strength
differences have been refuted by some researchers (Hunter, Critchlow, Shin, & Enoka, 2004;
Lindstrom, Lexell, Gerdle, & Downham, 1997). Some authors claim that weakness leads to
disuse atrophy and increased levels of fatigability (Edgerton, Roy, Allen, & Monti, 2002). A
secondary consequence of weakness and muscle atrophy is the recruitment of more motor units

41
or the greater frequency of excitation required to perform a given task. As a consequence of
recruiting more motor units, the overall fatigability will likely increase because increased
numbers of upper threshold units will be recruited, which include more fast fatiguing fibers.
Although these are all plausible theories, the relationship between absolute strength and muscle
fatigue is not fully understood and warrants further investigation.
Second, predominance of a particular fiber type can influence fatigue, as Type I (slow
twitch) fibers are more fatigue-resistant, while Type II (fast twitch) fibers are more fatigable
(Burke, Levine, Tsairis, & Zajac, 1973; Thorstensson & Karlsson, 1976). Decreased muscle
fatigue of children and the elderly as compared to adults has also been attributed to an increased
proportion of Type I, fatigue resistant fibers (Jansson, 1996; Larsson, Sjodin, & Karlsson, 1978).
Similarly, it has been postulated than a greater proportion of type II muscle fibers in men may
account for the greater fatigability of men compared to women observed in certain studies
(Bilodeau, Schindler-Ivens, Williams, Chandran, & Sharma, 2003). Although there are reports
of increased type I fibers in CP, there has been no consensus on fiber type predominance (Castle
et al., 1979; Ito et al., 1996; Marbini et al., 2002; Ponten, Friden, Thornell, & Lieber, 2005;
Romanini et al., 1989; Rose et al., 1994). These studies sampled muscle fibers across numerous
muscles and clinical presentations in addition to other methodological differences. Therefore, it
is not surprising that there is no general consensus on fiber type predominance. However, the
main results of this study could partially be explained if the disease process of CP does result in
muscle adaptations, which include increased proportions of Type I fibers. Other muscle
abnormalities in individuals with CP include collagen accumulation (Booth et al., 2001) and
increased stiffness at both the cellular (Friden & Lieber, 2003) and whole muscle level
(Hufschmidt & Mauritz, 1985). Perhaps, these muscle adaptations play a role in the development
of fatigue resistance as well.

42
Third, the issue of voluntary muscle activation must be considered. Lower voluntary
muscle activation in older adults has been postulated to contribute to differences in muscle
fatigue between older and younger adults (Bilodeau, Erb, Nichols, Joiner, & Weeks, 2001;
Stackhouse et al., 2001). Similarly, Stackhouse, Binder-Macleod, and Lee (2005) observed
voluntary muscle activation ratios of approximately 0.45 of the quadriceps and triceps surae in
children with CP ages 7 to 13 compared to 0.68 and 0.92, respectively, in age-matched typically
developing children. Therefore, despite the fact that the subjects with CP were giving 100%
effort, it is possible that they were not activating all of their motor units secondary to impaired
motor pathways. As a result, type I fibers may be preferentially recruited with lower firing rates,
contributing to the fatigue resistance. A limitation of the Stackhouse et al. (2005) study and
others that have examined voluntary or central activation ratios by means of twitch interpolation
is that voluntary activation is not assessed during the fatigue testing protocol. Therefore, it is
difficult to determine the extent to which voluntary activation levels contribute to the decline in
torque during the fatigue test. Further research is necessary to determine if there is a relationship
between level of voluntary muscle activation and muscle fatigue, as evidence for this theory is
lacking in the literature.
Differences in fatigability of the hamstrings measured during knee flexion and the
quadriceps measured during knee extension emerged across both groups. However, the
differences were not consistent for both fatigue parameters. According to the FI, the hamstrings
were more fatigable than the quadriceps. Conversely, the quadriceps were more fatigable than
the hamstrings, as indicated by a greater slope. This discrepancy may be due to the manner in
which the fatigue parameters are calculated.
The formula for the FI (%) can be reorganized as ∆PT / maximum torque. Thus, FI is
inversely influenced by the maximum PT values, where the slope is not, e.g. Slope = ∆PT /

43
∆Reps. The following theoretical discussion illustrates that extremely low PT could artificially
inflate FI values. The following torque values are approximated to the actual values for ease of
interpretation. For simplification, assume ∆ Reps equals 50 repetitions, and that the average of
the PT of the last 5 repetitions is theoretically equivalent to the PT of the last rep and that the
average of the highest consecutive 5 reps is equivalent to the first of the highest 5 reps. For the
quadriceps, the average PT of the last repetition was approximately 50 N-m, and the average PT
of the first of the highest 5 consecutive repetitions was 80 N-m, averaged across groups. This
would result in a slope of 0.6 and a FI of 37.5%, with a max torque of 80 and ∆PT of 30 N-m.
For the weaker hamstrings in this study, the average PT of the last repetition was 20 N-m, and
the average PT of the first of the highest 5 consecutive repetitions was 40 N-m. This would result
in a slope and FI of 0.4 and 66%, respectively, with a max torque of 40 and ∆PT of 20 N-m. It is
clear that the much lower maximum torque inversely influenced the FI, e.g., FI ∆ PT /
maximum torque. The slope, on the other hand, was only influenced by the magnitude of the
difference between the lowest and highest PT value, where Slope ∆ PT. Therefore, the slope
of the hamstrings was less than the quadriceps due to the smaller ∆ PT, but the FI was biased by
the much lower maximum torque of the hamstrings, resulting in a higher FI value. The
difference in the way the two parameters are calculated explains the discrepancy between the
results of the FI and slope for the effect of muscle groups (hamstrings and quadriceps). The same
trend was observed for the quadriceps and hamstrings when the fatigue parameters were
calculated separately for the group with CP and the control group. This observation is similar to
other studies that have shown the weaker hamstrings to be more fatigable than the quadriceps by
calculation of a FI in a healthy adult population (Gleeson & Mercer, 1992).
Most studies of muscle function in people with CP have focused on strength. However,
muscle endurance, or resistance to fatigue, is an important component of muscle performance

44
and has been overlooked in people with CP. Similar to studies of muscle strength, muscle
fatigue in this study was directly related to functional aspects, such as global functioning,
transfers and mobility, and sports and participation, and unrelated to psychosocial aspects.
However, the interpretation of these results is the converse (i.e., greater fatigue resistance, or
endurance, is predictive of lower levels of function and participation, as measured by the PODCI
and GMFCS). Until we understand the mechanisms behind the apparent fatigue resistance
observed in subjects with CP, we cannot fully understand the relationship between fatigue and
function.
In summary, the results of our study indicate that the knee flexors and extensors of
people with CP are less fatigable than age-matched peers without motor disability. In addition,
lower levels of muscle fatigability are associated with lower levels of function and participation.
These results suggest that a certain level of muscle fatigability is typical of a normally developed
muscle. It is postulated that the fatigue resistance may be attributed to weakness or lower
absolute torque levels, decreased voluntary activation, or muscle fiber type changes secondary to
hypertonia. However, further research is needed in order to explore these mechanisms and the
potential effect on muscle fatigability.
Reference List
Bar-Or, O., Dotan, R., & Inbar, O. (1977). 30-Sec All-Out Ergometric Test - Its Reliability and
Validity for Anaerobic Capacity. Israel Journal of Medical Sciences, 13, 326-327.
Barnes, W. S. (1980). The relationship between maximum isometric strength and intramuscular
circulatory occlusion. Ergonomics, 23, 351-357.
Bigland-Ritchie, B., Johansson, R., Lippold, O. C., & Woods, J. J. (1983). Contractile speed and
EMG changes during fatigue of sustained maximal voluntary contractions.
J.Neurophysiol., 50, 313-324.
Bilodeau, M., Erb, M. D., Nichols, J. M., Joiner, K. L., & Weeks, J. B. (2001). Fatigue of elbow
flexor muscles in younger and older adults. Muscle Nerve, 24, 98-106.
Bilodeau, M., Schindler-Ivens, S., Williams, D. M., Chandran, R., & Sharma, S. S. (2003).
EMG frequency content changes with increasing force and during fatigue in the

45
quadriceps femoris muscle of men and women. J Electromyogr.Kinesiol., 13, 83-92.

46
Booth, C. M., Cortina-Borja, M. J., & Theologis, T. N. (2001). Collagen accumulation in
muscles of children with cerebral palsy and correlation with severity of
spasticity. Dev.Med.Child Neurol., 43, 314-320.
Bottos, M., Feliciangeli, A., Sciuto, L., Gericke, C., & Vianello, A. (2001). Functional status of
adults with cerebral palsy and implications for treatment of children. Dev.Med.Child
Neurol., 43, 516-528.
Brusse, K. J., Zimdars, S., Zalewski, K. R., & Steffen, T. M. (2005). Testing functional
performance in people with Parkinson disease. Phys.Ther., 85, 134-141.
Burdett, R. G. & Van Swearingen, J. (1987). Reliability of isokinetic muscle endurance tests.
The Journal of Orthopaedic and Sports Physical Therapy, 8, 484-488.
Burke, R. E., Levine, D. N., Tsairis, P., & Zajac, F. E. (1973). Physiological types and
histochemical profiles in motor units of the cat gastrocnemius. Journal of Physiology
(London), 234, 723-748.
Castle, M. E., Reyman, T. A., & Schneider, M. (1979). Pathology of spastic muscle in cerebral
palsy. Clin.Orthop.Relat Res., 223-232.
Daltroy, L. H., Liang, M. H., Fossel, A. H., & Goldberg, M. J. (1998). The POSNA pediatric
musculoskeletal functional health questionnaire: report on reliability, validity, and
sensitivity to change. Pediatric Outcomes Instrument Development Group. Pediatric
Orthopaedic Society of North America. J.Pediatr.Orthop., 18, 561-571.
Damiano, D. L. & Abel, M. F. (1998). Functional outcomes of strength training in spastic
cerebral palsy. Arch.Phys.Med.Rehabil., 79, 119-125.
Damiano, D. L., Kelly, L. E., & Vaughn, C. L. (1995). Effects of quadriceps femoris muscle
strengthening on crouch gait in children with spastic diplegia. Phys.Ther., 75, 658-667.
De Ste Croix, M. B. A., Armstrong, N., & Welsman, J. R. (2003). The reliability of an isokinetic
knee muscle endurance test in young children. Pediatric Exercise Science, 15, 313-323.
Delitto, A. & Snyder-Mackler, L. (1990). Two theories of muscle strength augmentation using
percutaneous electrical stimulation. Phys.Ther., 70, 158-164.
Edgerton, V. R., Roy, R. R., Allen, D. L., & Monti, R. J. (2002). Adaptations in skeletal muscle
disuse or decreased-use atrophy. Am.J.Phys.Med.Rehabil., 81, S127-S147.
Friden, J. & Lieber, R. L. (2003). Spastic muscle cells are shorter and stiffer than normal cells.
Muscle Nerve, 27, 157-164.
Gleeson, N. P. & Mercer, T. H. (1992). Reproducibility of isokinetic leg strength and endurance
characteristics of adult men and women. Eur.J.Appl.Physiol Occup.Physiol, 65, 221-228.
Hoofwijk, M., Unnithan, V., & Bar-Or, O. (1995). Maximal treadmill performance of children
with cerebral palsy. Pediatric Exercise Science, 7, 305-313.

47
Hufschmidt, A. & Mauritz, K. H. (1985). Chronic transformation of muscle in spasticity: a
peripheral contribution to increased tone. J.Neurol.Neurosurg.Psychiatry, 48, 676-685.
Hunter, S. K., Critchlow, A., Shin, I. S., & Enoka, R. M. (2004). Men are more fatigable than
strength-matched women when performing intermittent submaximal contractions. J
Appl.Physiol, 96, 2125-2132.
Hunter, S. K. & Enoka, R. M. (2001). Sex differences in the fatigability of arm muscles depends
on absolute force during isometric contractions. J Appl.Physiol, 91, 2686-2694.
Ito, J., Araki, A., Tanaka, H., Tasaki, T., Cho, K., & Yamazaki, R. (1996). Muscle
histopathology in spastic cerebral palsy. Brain Dev., 18, 299-303.
Jahnsen, R., Villien, L., Egeland, T., Stanghelle, J. K., & Holm, I. (2004). Locomotion skills in
adults with cerebral palsy. Clin.Rehabil., 18, 309-316.
Jahnsen, R., Villien, L., Stanghelle, J. K., & Holm, I. (2003). Fatigue in adults with cerebral
palsy in Norway compared with the general population. Dev.Med.Child Neurol., 45, 296-
303.
Jansson, E. (1996). Age-related fiber type changes in human skeletal muscle. In R.J.Maughan &
S. M. Shireffs (Eds.), Biochemistry of Exercise IX (pp. 297-307). Champaign, IL: Human
Kinetics.
Jones & Stratton, G. (2000). Muscle function assessment in children. Acta Paediatr., 89, 753-
761.
Kanehisa, H., Okuyama, H., Ikegawa, S., & Fukunaga, T. (1995). Fatigability during repetitive
maximal knee extensions in 14-year-old boys. Eur.J Appl.Physiol Occup.Physiol, 72,
170-174.
Kramer, J. F. & MacPhail, H. E. (1994). Relationships among measures of walking efficiency,
gross motor ability, and isokinetic strength in adolescents with cerebral palsy. Pediatric
Physical Therapy, 6, 3-8.
Lambert, C. P., Archer, R. L., & Evans, W. J. (2001). Muscle strength and fatigue during
isokinetic exercise in individuals with multiple sclerosis. Med.Sci.Sports Exerc., 33,
1613-1619.
Lanza, I. R., Russ, D. W., & Kent-Braun, J. A. (2004). Age-related enhancement of fatigue
resistance is evident in men during both isometric and dynamic tasks. J Appl.Physiol, 97,
967-975.
Larsson, L., Sjodin, B., & Karlsson, J. (1978). Histochemical and biochemical changes in human
skeletal muscle with age in sedentary males, age 22--65 years. Acta Physiol Scand., 103,
31-39.

48
Lindstrom, B., Lexell, J., Gerdle, B., & Downham, D. (1997). Skeletal muscle fatigue and
endurance in young and old men and women. J Gerontol.A Biol.Sci Med Sci, 52, B59-
B66.
Lundberg, A. (1978). Maximal aerobic capacity of young people with spastic cerebral palsy.
Dev.Med.Child Neurol., 20, 205-210.
Marbini, A., Ferrari, A., Cioni, G., Bellanova, M. F., Fusco, C., & Gemignani, F. (2002).
Immunohistochemical study of muscle biopsy in children with cerebral palsy. Brain
Dev., 24, 63-66.
Moreau, N. G., Li, L., & Damiano, D. L. (2006). A feasible and reliable muscle fatigue protocol
for individuals with cerebral palsy. Manuscript submitted for publication.
Murphy, K. P., Molnar, G. E., & Lankasky, K. (1995). Medical and functional status of adults
with cerebral palsy. Dev.Med.Child Neurol., 37, 1075-1084.
Palisano, R., Rosenbaum, P., Walter, S., Russell, D., Wood, E., & Galuppi, B. (1997).
Development and reliability of a system to classify gross motor function in children with
cerebral palsy. Dev.Med.Child Neurol., 39, 214-223.
Parker, D. F., Carriere, L., Hebestreit, H., & Bar-Or, O. (1992). Anaerobic endurance and peak
muscle power in children with spastic cerebral palsy. Am.J.Dis.Child, 146, 1069-1073.
Parker, D. F., Carriere, L., Hebestreit, H., Salsberg, A., & Bar-Or, O. (1993). Muscle
performance and gross motor function of children with spastic cerebral
palsy. Dev.Med.Child Neurol., 35, 17-23.
Pincivero, D. M., Gandaio, C. M., & Ito, Y. (2003). Gender-specific knee extensor torque, flexor
torque, and muscle fatigue responses during maximal effort contractions.
Eur.J.Appl.Physiol, 89, 134-141.
Pincivero, D. M., Gear, W. S., & Sterner, R. L. (2001). Assessment of the reliability of high-
intensity quadriceps femoris muscle fatigue. Med.Sci.Sports Exerc., 33, 334-338.
Pirpiris, M., Gates, P. E., McCarthy, J. J., D'Astous, J., Tylkowksi, C., Sanders, J. O. et al.
(2006). Function and well-being in ambulatory children with cerebral palsy. J
Pediatr.Orthop., 26, 119-124.
Ponten, E., Friden, J., Thornell, L. E., & Lieber, R. L. (2005). Spastic wrist flexors are more
severely affected than wrist extensors in children with cerebral palsy. Dev.Med.Child
Neurol., 47, 384-389.
Romanini, L., Villani, C., Meloni, C., & Calvisi, V. (1989). Histological and
morphological aspects of muscle in infantile cerebral palsy.
Ital.J.Orthop.Traumatol., 15, 87-93.
Rose, J., Haskell, W. L., & Gamble, J. G. (1993). A comparison of oxygen pulse and respiratory
exchange ratio in cerebral palsied and nondisabled children. Arch.Phys.Med.Rehabil., 74,
702-705.

49
Rose, J., Haskell, W. L., Gamble, J. G., Hamilton, R. L., Brown, D. A., & Rinsky, L. (1994).
Muscle pathology and clinical measures of disability in children with cerebral palsy.
J.Orthop.Res., 12, 758-768.
Stackhouse, S. K., Binder-Macleod, S. A., & Lee, S. C. (2005). Voluntary muscle activation,
contractile properties, and fatigability in children with and without cerebral palsy. Muscle
Nerve, 31, 594-601.
Stackhouse, S. K., Stevens, J. E., Lee, S. C., Pearce, K. M., Snyder-Mackler, L., & Binder-
Macleod, S. A. (2001). Maximum voluntary activation in nonfatigued and fatigued
muscle of young and elderly individuals. Phys.Ther., 81, 1102-1109.
Thorstensson, A. & Karlsson, J. (1976). Fatiguability and fibre composition of human skeletal
muscle. Acta Physiol Scand., 98, 318-322.
Tirosh, E., Bar-Or, O., & Rosenbaum, P. (1990). New muscle power test in
neuromuscular disease. Feasibility and reliability. Am.J.Dis.Child, 144, 1083-
1087.
Tobimatsu, Y., Nakamura, R., Kusano, S., & Iwasaki, Y. (1998). Cardiorespiratory endurance in
people with cerebral palsy measured using an arm ergometer. Arch.Phys.Med.Rehabil.,
79, 991-993.
Unnithan, V. B., Dowling, J. J., Frost, G., & Bar-Or, O. (1996). Role of cocontraction in the O2
cost of walking in children with cerebral palsy. Med.Sci.Sports Exerc., 28, 1498-1504.
Wood, E. & Rosenbaum, P. (2000). The gross motor function classification system for cerebral
palsy: a study of reliability and stability over time. Dev.Med.Child Neurol., 42, 292-296.

50
CHAPTER 4: MUSCLE FATIGUE IN CEREBRAL PALSY: RELATIONSHIP
TO SPASTICITY, STRENGTH, STIFFNESS, AND COCONTRACTION
Introduction
Muscle fatigue, or fatigability, is defined as a reduction in force output that occurs during
sustained activity (Bigland-Ritchie, Johansson, Lippold, & Woods, 1983). Debate over the
mechanisms responsible for lower levels of muscle fatigue, known as fatigue resistance, in
certain populations has been the topic of discussion for many years. For example, greater fatigue
resistance has been observed in children and healthy older adults compared to young adults and
females compared to males. Despite the fact that the results are equivocal, several mechanisms
have been proposed to explain the fatigue resistance, primarily differences in the following:
muscle mass, muscle morphology, voluntary activation, patterns of motor unit recruitment and
rate modulation, and energy metabolism or substrate utilization (Lanza, Russ, & Kent-Braun,
2004; Pincivero, Gandaio, & Ito, 2003; Ratel, Lazaar, Williams, Bedu, & Duche, 2003).
We have shown in a previous study that the knee flexors and extensors in children and
young adults with cerebral palsy (CP) are more fatigue resistant than those of typically
developing peers (Moreau, Li, & Damiano, 2006b). In addition to the aforementioned factors,
there are additional factors related to neurological injury that may play a significant role in the
fatigue-resistance observed in our sample of subjects with CP. Factors that may contribute to
muscle fatigue are weakness, cocontraction, spasticity, and stiffness. CP is a multifaceted
disorder and as such, complex interrelationships exist among upper motor neuron lesion
impairments. The relationships between muscle fatigue and other impairments are important in
the understanding of fatigue, as these impairments may, in fact, contribute directly or indirectly
to the level of muscle fatigability.
It is well-recognized that many children with CP have spasticity, or a velocity-dependent
increased resistance to movement due to hyperexcitable stretch reflexes (Lance, 1980). Although

51
the primary lesion of CP is neural, it is important to discuss the properties of spastic muscle
because muscles adapt to the amount and type of neural stimulation that is imposed upon them.
In general, fiber type distribution and muscle fiber size are indicators of the amount and type of
activity imposed upon a muscle and as such, are often investigated in spastic muscle in order to
determine a muscle’s usage pattern (Lenman, Tulley, Vrbova, Dimitrijevic, & Towle, 1989;
Miller, Green, Moussavi, Carson, & Weiner, 1990; Rose et al., 1994). Predominance of a
particular fiber type can influence fatigue, as Type I (slow twitch) fibers are more fatigue-
resistant while Type II (fast twitch) fibers are more fatigable (Burke, Levine, Tsairis, & Zajac,
1973; Thorstensson & Karlsson, 1976). Therefore, investigation of the muscle adaptations which
may occur secondary to spasticity has provided insight into the effects of the disease process on
muscle characteristics over an extended period of time (Lieber, Steinman, Barash, & Chambers,
2004). Several authors have reported increased percentages of type I fibers in children with CP
(Ito et al., 1996; Marbini et al., 2002; Rose et al., 1994). If greater loss or transformation of Type
II to Type I fibers occurs as a secondary adaptation to spasticity, then this could contribute to
lower levels of fatigability. However, the results are not conclusive as there have also been
reports of no differences in fiber type (Castle, Reyman, & Schneider, 1979; Romanini, Villani,
Meloni, & Calvisi, 1989). These studies sampled fibers across numerous muscles in addition to
other methodological differences, so it is not surprising that there are discrepancies.
Furthermore, spasticity may not affect certain muscles while affecting others to varying degrees
within and between individuals, so it is important to document both the presence and magnitude
of spasticity for the muscles under investigation.
Other muscle abnormalities which may play a role in the development of fatigue
resistance in individuals with CP include excessive collagen accumulation (Booth, Cortina-
Borja, & Theologis, 2001) and increased stiffness at both the cellular (Friden & Lieber, 2003)

52
and whole muscle level (Hufschmidt & Mauritz, 1985). Stiffness is defined as a length-
dependent resistance to movement and quantified as the slope of the torque/angle curve. It has
been suggested that increased stiffness may be a compensation for weakness, thus allowing
better utilization of elastic energy during functional activities, such as gait (Lamontagne,
Malouin, & Richards, 2000; Svantesson & Sunnerhagen, 1997). Therefore, stiffness may also
contribute to fatigue resistance through altered mechanical properties of muscle.
Strength deficits as high as 50% or greater have been well documented in children with
CP. The exact nature of the weakness is unclear and is thought to be a result of either decreased
central drive to the agonist due to the lesion itself, spasticity, cocontraction, secondary changes
in the properties of the muscles fibers, or some combination of the above (Damiano, Quinlivan,
Owen, Shaffrey, & Abel, 2001). Cocontraction refers to the simultaneous activation of agonist
and antagonist muscles during voluntary movement. Cocontraction, in particular, may impair
the full activation of the agonist due to reciprocal inhibition, leading to weakness (Milner,
Cloutier, Leger, & Franklin, 1995; Tyler & Hutton, 1986). Differences in strength have been
postulated to explain the differences in fatigability observed between older and younger adults
(Hunter & Enoka, 2001; Pincivero et al., 2003), children and young adults (Kanehisa, Okuyama,
Ikegawa, & Fukunaga, 1995), and females and males (Hunter & Enoka, 2001; Pincivero et al.,
2003). The muscle mass or strength hypothesis states that stronger subjects would have more
blood flow occlusion than weaker subjects at the same relative load, particularly during
isometric tasks, leading to higher levels of fatigability (Barnes, 1980). Still others feel that
stronger individuals have a higher susceptibility to fatigue due to the ability to generate higher
absolute torque levels (Pincivero et al., 2003).
Although we have previously shown that the knee flexors and extensors in people with
CP are less fatigable than typically developing peers, possible contributors to the fatigue

53
resistance have yet to be investigated. Therefore, the purpose of this study was to quantify
spasticity, stiffness, cocontraction, and strength of the quadriceps and hamstrings in a group of
subjects with mild to moderate CP in order to determine whether these variables are associated
with fatigue-resistance of these muscle groups. We hypothesized that subjects with spasticity
would have lower levels of muscle fatigability. In addition, we hypothesized that the magnitude
of spasticity would be inversely related to the amount of muscle fatigue in the spastic muscle.
For example, those with spasticity of the hamstrings would have lower levels of muscle fatigue
of the hamstrings compared to those without hamstring spasticity. Furthermore, higher
magnitudes of spasticity as measured by resistive torque would be associated with lower levels
of muscle fatigue. Due to the interrelationships of muscle weakness with stiffness and
cocontraction, we also hypothesized that higher levels of weakness, stiffness, and cocontraction
would be associated with lower levels of muscle fatigue about the knee joint.
Methods
Participants
Seventeen subjects with cerebral palsy (CP) between the ages of 10 and 25 were recruited
for the study. Physical demographics of the subjects are listed in Table 4.1. All subjects were
able to ambulate at least a short distance with or without assistive devices. Subjects were
excluded if they underwent orthopedic surgery within 12 months prior to the testing, received
Botulinum toxin injections to the quadriceps or hamstrings within 6 months prior to the testing,
or suffered from knee pain. Passive range of motion of the knee was also assessed prior to testing
to determine if the subject had sufficient range of motion to complete the test. A control group of
14 subjects without motor disability (ages 10-24) was used for comparison and illustrative
purposes.

54
Table 4.1
Physical Demographics
Age GMFCS
Sex range mean/sd Height (m) Weight (kg) I II III
CP 12F/5M 10 - 23 17.5 ± 5.0 1.5 ± 0.1 47.6 ± 9.9 9 5 3
Control 11F/3M 10 - 23 16.6 ± 4.4 1.6 ± 0.1 54.0 ± 9.7 na Na na
M = male; F = female; na = not applicable
The study was approved by the Institutional Review Board at our institution. A written
consent form was obtained from each participant over 18 years of age. A parental permission
form signed by one parent or legal guardian was required for participants under 18 years of age.
In addition, the minor was required to read and sign a child assent form (APPENDIX 2).
Instruments
Isokinetic Dynamometry
An isokinetic dynamometer (Biodex Medical Systems Incorporated, Shirley, NY, USA)
was used to collect angular displacement, angular velocity, and torque data for both the passive
and active trials. These were then used to calculate strength, spasticity, stiffness, and muscle
fatigue of the knee flexors and extensors. Consistent throughout the paper, the terms knee
extension and flexion will refer to the direction of motion, regardless of whether the trial was
active or passive.
Electromyography
Surface electromyography (EMG) of the lateral hamstrings and quadriceps was
collected with the MA-300 EMG system (Motion Lab Systems, Baton Rouge, LA, USA). The
skin of the participant was cleansed and abraded with alcohol prep pads before placement of the
electrodes. The Ag-AgCl bipolar electrode pair was positioned one-third of the distance
between the ischial tuberosities and the popliteal crease on the muscle bellies of the biceps

55
femoris and

56
semitendinosus. The circular 1.0 cm diameter electrode pair was positioned 2.0 cm, center to
center, from each other and longitudinally along the muscles. The MA-311 (Motion Lab
Systems, Baton Rouge, LA, USA) surface EMG pre-amplifiers were placed on the muscle
bellies of the rectus femoris and vastus medialis, on the proximal and distal one-third of the
distance between the anterior iliac superior spine and the patella, respectively. A ground
electrode was placed on the anterolateral surface of the participant’s upper thigh. Proper
electrode placement was verified through use of the WinDaq Acquisition software (Dataq
Instruments, Dayton, OH, USA) in conjunction with manual muscle testing of each muscle. The
bandpass width used for collection was 0 – 500 Hz, and the signal was sampled at 1000 Hz per
channel with an amplification of up to 20,000. The common mode rejection ratio (CMRR) was
100 dB. The EMG was collected using a 12 bit analog to digital conversion board via the EMG
system and saved for future processing. Angular displacement, angular velocity, and torque data
from the dynamometer were collected with the EMG data and internally synchronized using the
WinDaq Acquisition software.
Protocol
Setup
The electrodes were positioned as described above. The subject was positioned in the
Biodex chair in a semireclining sitting position with the thigh horizontal and trunk 70 degrees
above horizontal. The more involved lower extremity was tested for subjects with bilateral or
unilateral involvement if they had sufficient motion and mobility in that limb to perform the test.
The left lower extremity was tested for control subjects. The subject’s knee joint center was
aligned with the center of rotation of the isokinetic device. The leg was secured against the knee
attachment pad and additional stabilizing straps around the waist, the trunk, and over the mid-
thigh portion were used to restrain trunk and hip movement during testing. The passive range of

57
motion designated as “comfortable” by the patient was determined and used to set the limits of
motion for the rest of testing sessions. Subjects were instructed to keep their arms folded across
their chest for all trials.
Isokinetic Passive Testing
The passive testing consisted of repeated extension and flexion of the knee within the
preset range of motion with a 1 second pause during the reversal of motion. The subjects were
instructed to relax their muscles. Surface EMG of the quadriceps and hamstrings were monitored
during the test to provide verification that the muscles were not active. Three passive repetitions
were performed at 5, 10, 30, 60, 90, and 120 degrees/second. A 30 second rest period was
provided between each velocity. Peak resistive torque (RT) was calculated for both knee flexion
and extension motions (Damiano et al., 2002; Damiano et al., 2001).
Isokinetic Strength Testing
The subjects performed 5-10 submaximal concentric, reciprocal knee flexion and
extension repetitions to familiarize themselves with the procedure. The subjects then performed
3 maximal concentric exertions for each muscle group at 60 degrees per second. One minute of
rest was given between repetitions to minimize muscle fatigue (Damiano et al., 2001). The
subjects were instructed to “push” and “pull” their leg against the lever as hard as possible.
Verbal encouragement and visual feedback of the torque value presented on the monitor was
used to encourage maximum effort.
Isokinetic Fatigue Testing
Five minutes of rest was given prior to the muscle fatigue protocol. The fatigue protocol
consisted of reciprocal, maximal concentric knee extension and flexion at 60 degrees/second for
35 repetitions. This protocol was shown to be feasible in a group of subjects with mild to
moderate CP (Moreau, Li, & Damiano, 2006a). The subjects were instructed to “push” and

58
“pull” their leg against the lever as hard as possible. Strong verbal encouragement was given for
every repetition to encourage maximal effort on all repetitions. The subject was able to
terminate the test at any time either verbally or through use of a safety switch.
Data Analysis
Spasticity
Table 4.2 lists all of the abbreviations used to identify variables by category in the data
analysis. Only data in the constant velocity portion of the passive trials were analyzed, thereby
negating the effects of inertia. Gravity correction calculation of the limb’s weight was taken
between 30 and 45 degrees of knee flexion in order to remove the gravitational effects of the
limb and attachment from each trial. The algorithm provided by the Biodex Advantage Software
Operations Manual (Version 3.29/3.30) was utilized for the gravity correction. Spasticity was
measured as the peak resistive torque (RT) during the isokinetic portion of the range at 60 and
120 degrees/second, with EMG verification of a stretch response. 60 degrees/second was chosen
because the voluntary tests of strength and muscle fatigue were tested at this speed. Due to the
velocity dependent nature of spasticity, the fastest speed of 120 degrees/second was also chosen
as a representative measure of spasticity. Spasticity of the hamstrings was measured as the peak
RT during passive knee extension (RTH), and spasticity of the quadriceps was measured as the
peak RT during passive knee flexion (RTQ).
EMG data were used to verify the presence or absence of a stretch response, or spasticity,
during each passive trial at 30, 60, 90, and 120 degrees/second separately for the hamstrings and
quadriceps. Participants were categorized by whether or not they demonstrated hamstrings or
quadriceps stretch responses. The speed at which the stretch response began, or the velocity
threshold, was recorded for each subject (Damiano et al., 2002; Damiano et al., 2001).

59
Table 4.2
List of abbreviations (by category) used to identify the various variables
Variables (units) Description
Universal
KE Knee extension
KF Knee flexion
PT (N·m) Peak torque
Fatigue variables
Slope PTQ (N·m·rep-1) Slope of the decline in quadriceps PT (KE) over 35 reps
Slope PTH (N·m·rep-1) Slope of the decline in hamstring PT (KF) over 35 reps
FIQ (% decline) Fatigue index of quadriceps (% decline in PTKE) over 35
reps FIH (% decline) Fatigue index of hamstrings (% decline in PTKF) over 35 reps
Strength variables
PTQ (N·m) Strength (PT) of the quadriceps during active KE
PTH (N·m Strength (PT) of the hamstrings during active KF
FatPTQ (N·m) PT of quadriceps over all KE repetitions of the fatigue test
FatPTH (N·m) PT of hamstrings over all KF repetitions of the fatigue test
Spasticity
RT (N·m) Resistive torque
RTQ60 and RTQ120 (N·m) Peak RT of the quadriceps during passive KF at 60 and 120
degrees/second, respectively
RTH60 and RTH120 (N·m) Peak RT of the hamstrings during passive KE at 60 and 120
degrees/second, respectively
Stiffness
StiffQ5, StiffQ30, StiffQ60,
StiffQ90 (N·m·deg-1)
StiffH5, StiffH30, StiffH60,
StiffH90 (N·m·deg-1)
Cocontraction
Stiffness of quadriceps (slope of torque/angle curve) measured
during passive KF at 5, 30, 60, & 90 deg/sec, respectively
Stiffness of hamstrings (slope of torque/angle curve)
measured during passive KE at 5, 30, 60, & 90 deg/sec,
respectively
CoconQ (%) Cocontraction of quads as % of activity working as an agonist
CoconH (%) Cocontraction of hams as % of activity working as an agonist
Stiffness
Gravity correction and removal of the acceleration and deceleration phases of the trials
were performed as described above. Passive tissue properties can be characterized as viscoelastic
(Lehmann, Price, deLateur, Hinderer, & Traynor, 1989). Passive elastic stiffness was measured
by the slope of the resistance torque by angle curve during the constant velocity portion of the 5
degree per second passive trial in the absence of EMG activity. Simultaneous collection of

60
surface EMG of the quadriceps and hamstrings provided verification that the muscles were not
active during this slow, passive trial. The slow speed was used in order to minimize the effect of
velocity and reflexive activity (Lee, Huang, Chen, & Hwang, 2002). In this manner, the
resistance provided by the passive mechanical properties of the tissues, such as non-active
muscle tissue, joint capsule, and surrounding connective tissue was measured. For
simplification, stiffness measured during knee extension will be referred to as stiffness of the
hamstrings (StiffH), and stiffness measured during knee flexion will be referred to as stiffness of
the quadriceps (StiffQ). To provide a measure of velocity-dependency, stiffness was also
calculated as the slope of the resistance torque by angle curve at 30, 60 and 90 degrees/second
(Damiano et al., 2001). Both reflexive and elastic stiffness play a role in those with spastic
responses at these higher velocities. We were unable to calculate stiffness at 120 degrees/second
in the majority of subjects secondary to the truncated constant velocity range.
Cocontraction
The recorded EMG data from the strength assessment were full-wave rectified and
smoothed with a low pass filter at 6 Hz using a fourth-order zero lag Butterworth filter. The
filtered EMG was separated into a flexion and extension phase during the isokinetic portion and
the mean absolute value (MAV) was calculated. Hamstring cocontraction (CoconH) during the
maximal knee extension contraction was calculated as the ratio of the MAV of the biceps
femoris EMG activity during the extension phase to the EMG activity during the flexion phase,
multiplied by 100. Quadriceps cocontraction (CoconQ) during the maximal knee flexion
contraction was calculated as the ratio of the MAV of the rectus femoris EMG activity during
the flexion phase to the EMG activity during the extension phase, multiplied by 100 (Baratta et
al., 1988; Weir, Keefe, Eaton, Augustine, & Tobin, 1998).

61
Strength
Torque data from the strength assessment were also gravity corrected and only the
constant velocity portion was used. Voluntary peak torque (PT) was calculated for each of the 3
repetitions of the strength test for both extension and flexion. The maximum of these values over
the 3 repetitions was the measure of strength for each muscle group (Damiano et al., 2001).
Strength of the quadriceps (StrPTQ) was measured as the voluntary PT during knee extension.
Strength of the hamstrings (StrPTH) was measured as the voluntary PT during knee flexion. The
maximum PT over the 35 repetitions of the fatigue protocol was also recorded as a measure of
strength for the quadriceps (FatPTQ) and the hamstrings (FatPTH).
Fatigue
Two accepteded measures of fatigue were computed: 1.) percent decline in peak torque
over the 35 repetitions, calculated as a Fatigue Index (FI) (Pincivero et al., 2003):
FI 100
PT last 5 reps x 100%
PT highest 5 reps
2.) rate of decline in PT represented by the slope of the linear regression, beginning with the first
value of the highest 5 consecutive repetitions and ending with the last repetition (Pincivero,
Gear, & Sterner, 2001). Because FI and slope calculations began with the first value of the
highest 5 consecutive repetitions, the protocol was extended to 50 repetitions in subjects when
the initial highest torque value occurred later than the 15th repetition. Torque data from the
fatigue protocol were gravity corrected and only the constant velocity portion was used as
described previously. Fatigue of the quadriceps muscle group was measured as the FI (FIQ) and
slope (SlopePTQ) calculated during knee extension, and fatigue of the hamstrings was measured
as the FI (FIH) and (SlopePTH) during knee flexion. This fatigue protocol was previously
shown to be reliable in children and young adults with mild to moderate CP (Moreau et al.,
2006a).

62
Statistical Analyses
Linear regression was used to determine the relationships between the fatigue parameters
(slope and FI) and stiffness, spasticity, strength, and cocontraction for both knee extension and
flexion. Stepwise multiple regression analyses were performed in order to identify which of
these factors or combination of factors best explained the variations in fatigability. The
dependent variables were the FI and slope for the knee extensors and flexors. Measures of
stiffness, spasticity, strength, and co-contraction were entered as independent variables. The
criterion for entry into the regression equation and removal was p < 0.05. An R-Square selection
option was also run to see if other combinations of variables predicted similar amounts of
variance as the resulting step-wise regression models. For example, if a two factor model was
predicted by the step-wise multiple regression analysis, then other two factor models were
compared to see if a similar amount of variance could be explained with a different combination
of variables. One- way ANOVA was used to test for differences in fatigability between subjects
with and without hamstring and quadriceps spasticity and control subjects. Tukey’s HSD was
used for post-hoc analysis. Finally, t-tests were used to test for differences in the peak torque
obtained from the strength test versus the fatigue protocol for both muscle groups.
Results
The maximum torque during the fatigue test occurred between the 3rd and 27th repetition
for the knee extensors (9.3 ± 7.2) and between the 1st and 20th repetition for the knee flexors (5.0
± 6.1) for the group with CP. In the control group, the maximum torque during the fatigue test
occurred on average during the 3rd repetition for both knee extension (3.4 ± 2.1) and knee flexion
(3.4 ± 3.7). As illustrated in Table 4.3, maximum peak torque of the quadriceps obtained during
the strength test (PTQ) was significantly less than the maximum torque obtained during the
fatigue test (FatPTQ) for the group with CP. However, values from the two tests for the
63
hamstrings were similar. No significant differences between the PT values of the strength and
fatigue tests were observed in the control group for either muscle (Table 4.3). Because strength
of the quadriceps in the group with CP was underestimated by PTQ in this study and a previous
study (Moreau et al., 2006a), the PT values obtained during the fatigue test were used in
subsequent analyses as the measure of strength. After normalizing strength by body weight, the
subjects with CP were on average 40% and 60% weaker than the age-matched control group for
the quadriceps and hamstrings, respectively.
Table 4.3
Comparison of voluntary peak torque obtained
during the strength versus the fatigue test
Strength Fatigue
test test
CP
Quad 41.2 ± 3.9 55.0 ± 5.1*
nQuad 89.9 ± 8.9 120.9 ± 12.0*
Hams 22.8 ± 3.2 23.9 ± 2.8
nHams 49.8 ± 6.8 52.3 ± 6.2
Control
Quad 110.2 ± 8.8 113.0 ± 9.5
nQuad 197.4 ± 10.9 200.9 ± 11.9
Hams 63.0 ± 6.4 60.2 ± 5.5
nHams 111.7 ± 8.5 107.0 ± 6.9
Peak torque (PT) given in N-m ; * = p < .0001;
Quad = PT obtained during knee extension; Hams = PT
obtained during knee flexion; nQuad = Quad normalized by
body weight; nHams = Hams normalized by body weight
Regression Analyses
Figures 4.1 and 4.2 illustrate the means and SEM of the stiffness and RT values,
respectively, for the quadriceps and hamstrings. Figure 4.3 illustrates the means and SEM of the
cocontraction values of the quadriceps (CoconQ) and hamstrings (CoconH). The results of both
the linear and stepwise multiple regression analyses for the slope of the quadriceps (SlopePTQ)
as a measure of fatigue are presented in Table 4.4. Strength of the hamstrings and quadriceps
CPControl
CPControl
64
a.) b.)
0.4 0.4
0.3 0.3
0.2 0.2
0.1 0.1
0
5 30 60 90
Hamstrings
0
5 30 60 90
Quadriceps
Figure 4.1. Mean and SEM of a.) hamstring stiffness and b.) quadriceps stiffness at 5, 30, 60,
and 90 degrees/second for the group with CP and the control group.
a.) b.)
12 12
88
4 4
0
60 120
Hamstrings
0
60 120
Quadriceps
Figure 4.2. Mean and SEM of a.) resistance torque (RT) of the hamstrings and b.) RT of the
quadriceps at 60 and 120 degrees/second as a measure of spasticity for the group with CP and the
control group.
Stiffness (N·m·deg-1)
RT (N·m)

100 CPControl
75
50
25
65
0
Hamstrings Quadriceps
Figure 4.3. Cocontraction of the hamstrings (CoconH) and quadriceps (CoconQ) for the group
with CP and the control group.
Table 4.4
Linear and stepwise multiple regression analysis of variables potentially related to muscle fatigue
of the knee extensors as represented by the slope of the decline in peak torque across repetitions
(SlopePTQ).
Variables Linear regression p
coefficient (r) Multiple linear Partial Model
regression R-square R-square p
parameter est.
FatPTQ 0.69 0.002 - - - -
FatPTH 0.74 0.001 - - - -
StiffH5 0.31 0.22 - - - -
StiffH30 0.20 0.44 - - - -
StiffH60 0.16 0.53 - - - -
StiffH90 0.15 0.58 - - - -
StiffQ5 -0.49 0.04 - - - -
StiffQ30 -0.43 0.08 - - - -
StiffQ60 -0.36 0.15 - - - -
StiffQ90 -0.64 0.02 - - - -
RTH60 0.20 0.45 - - - -
RTH120 -0.06 0.83 - - - -
RTQ60 -0.17 0.53 - - - -
RTQ120 -0.13 0.64 - - - -
CoconH -0.57 0.02 -0.004 0.43 0.43 0.03
CoconQ -0.54 0.03 - - - -
est. = estimate
Cocontraction (%)

66
(FatPTH and FatPTQ) were positively correlated to the SlopePTQ, where those who were
weaker had lower levels of muscle fatigue of the quadriceps. CoconH and CoconQ were
inversely correlated to the SlopePTQ, where higher cocontraction was related to lower levels of
quadriceps fatigability. Stiffness of the quadriceps at both 5 (StiffQ5) and 90 (StiffQ90)
degrees/second were also inversely correlated to SlopePTQ, such that increased stiffness of the
quadriceps was related to lower levels fatigability of the quadriceps. Although strength, stiffness,
and cocontraction of both muscle groups were related to fatigability of the quadriceps in the
univariate analysis, CoconH was the only significant predictor of SlopePTQ in the multiple
regression analysis, explaining 43% of the variance. Both univariate linear regression
coefficients and parameter estimates indicate that increased levels of cocontraction of the
antagonistic hamstrings muscle group are associated with lower levels of quadriceps fatigability.
No other single factor models predicted a similar amount of variance in SlopePTQ.
Table 4.5 illustrates the results of both the linear and stepwise multiple regression
analyses for the slope as a measure of fatigue of the hamstrings (SlopePTH). Similarly, FatPTH
and FatPTQ were positively correlated to the SlopePTH, where weaker individuals had lower
levels of hamstring fatigability. Likewise, StiffQ5, StiffQ90, and CoconH were inversely related
to fatigability of the hamstrings. Multiple regression analysis revealed that FatPTH and StiffQ5
were significant predictors of hamstring fatigability as measured by SlopePTH, explaining a total
of 72% of the variance. Univariate linear regression coefficients and parameter estimates indicate
that weaker hamstrings and stiffer quadriceps are associated with lower levels of hamstring
fatigability. No other two factor models predicted a similar amount of variance in SlopePTH.
None of the variables in the univariate linear regression analysis were significantly
correlated with the FI of the quadriceps (FIQ), although CoconH approached significance (r = -
0.49, p = 0.056). Only StiffQ90 displayed a significant inverse relationship to FI of the

67
hamstrings (FIH: r = -0.68, p = 0.01). Because only one variable was correlated with FIH and
none with FIQ, multiple regression analyses were not performed for these variables, and
subsequent analyses were only performed on the fatigue slope values.
Table 4.5
Linear and stepwise multiple regression analysis of variables potentially related to muscle fatigue of
the knee flexors as represented by the slope of the decline in peak torque across repetitions
(SlopePTH).
est. = estimate
Presence of Spasticity
Out of the 17 subjects with CP, 10 had hamstring spasticity only, none had quadriceps
spasticity only, 4 had quadriceps and hamstrings spasticity, and 3 had no spasticity of either
muscle group. Spastic or reflexive stretch responses were detected at 30 degrees/second in 13 of
the18 muscles with spasticity. In the remaining 5 muscle groups, stretch responses were detected
at 60 degrees/second in 4 and at 120 degrees/second in 1. All subjects who demonstrated a
spastic response at a lower velocity also demonstrated a response at the higher velocities. A
Variables Linear regression p
coefficient (r) Multiple linear Partial Model
regression R-square R-square p
parameter est.
FatPTQ 0.54 0.02 - - - -
FatPTH 0.78 0.001 0.01 0.27 0.27 0.02
StiffH5 0.27 0.30 - - - -
StiffH30 0.06 0.81 - - - -
StiffH60 0.15 0.56 - - - -
StiffH90 0.13 0.62 - - - -
StiffQ5 -0.49 0.04 -5.60 0.45 0.72 0.02
StiffQ30 -0.24 0.36 - - - -
StiffQ60 -0.22 0.40 - - - -
StiffQ90 -0.72 0.01 - - - -
RTH60 0.10 0.70 - - - -
RTH120 -0.11 0.68 - - - -
RTQ60 -0.30 0.27 - - - -
RTQ120 -0.15 0.59 - - - -
CoconH -0.52 0.04 - - - -
CoconQ -0.42 0.11 - - - -

68
significant difference was observed between groups for both quadriceps (F3,27 = 13.04, p <
0.0001) and hamstring (F3,27 = 10.09, p < 0.0001) fatigability as measured by the slope. Post hoc
analyses reveal significant differences between the control group without disability and the two
groups with spasticity for SlopePTQ and Slope PTH as illustrated in Figures 4.4a and 4.4b,
respectively. The control group was more fatigable than the two groups with spasticity.
However, there were no significant differences between the control group and the group without
spasticity for both SlopePTQ and SlopePTH, nor were there any differences between the 3
groups with CP.
Discussion
Results of this study indicate that strength, spasticity, stiffness, and cocontraction are
related to muscle fatigability of the quadriceps and hamstrings, as measured by the slope. More
specifically, strength was directly related to muscle fatigability, where weaker subjects had lower
levels of fatigability, regardless of muscle. Cocontraction and quadriceps stiffness, on the other
hand, were inversely related to muscle fatigability, where higher cocontraction and quadriceps
stiffness yielded lower levels of hamstrings and quadriceps fatigue. When controlling for
confounding variables in the multiple regression analysis, the strongest predictors of hamstring
fatigability were hamstrings strength and quadriceps stiffness (StiffQ5). A positive relationship
of hamstrings strength and an inverse relationship of quadriceps stiffness (StiffQ5) to hamstring
yielded lower levels of hamstring fatigability. When controlling for confounding variables in the
multiple regression analysis, the strongest predictor of quadriceps fatigability was hamstring
cocontraction. An inverse antagonistic relationship of hamstring cocontraction to quadriceps
fatigability was observed, where increased cocontraction of the hamstrings was related to lower
levels of quadriceps fatigability. Furthermore, the presence of spasticity was also able to
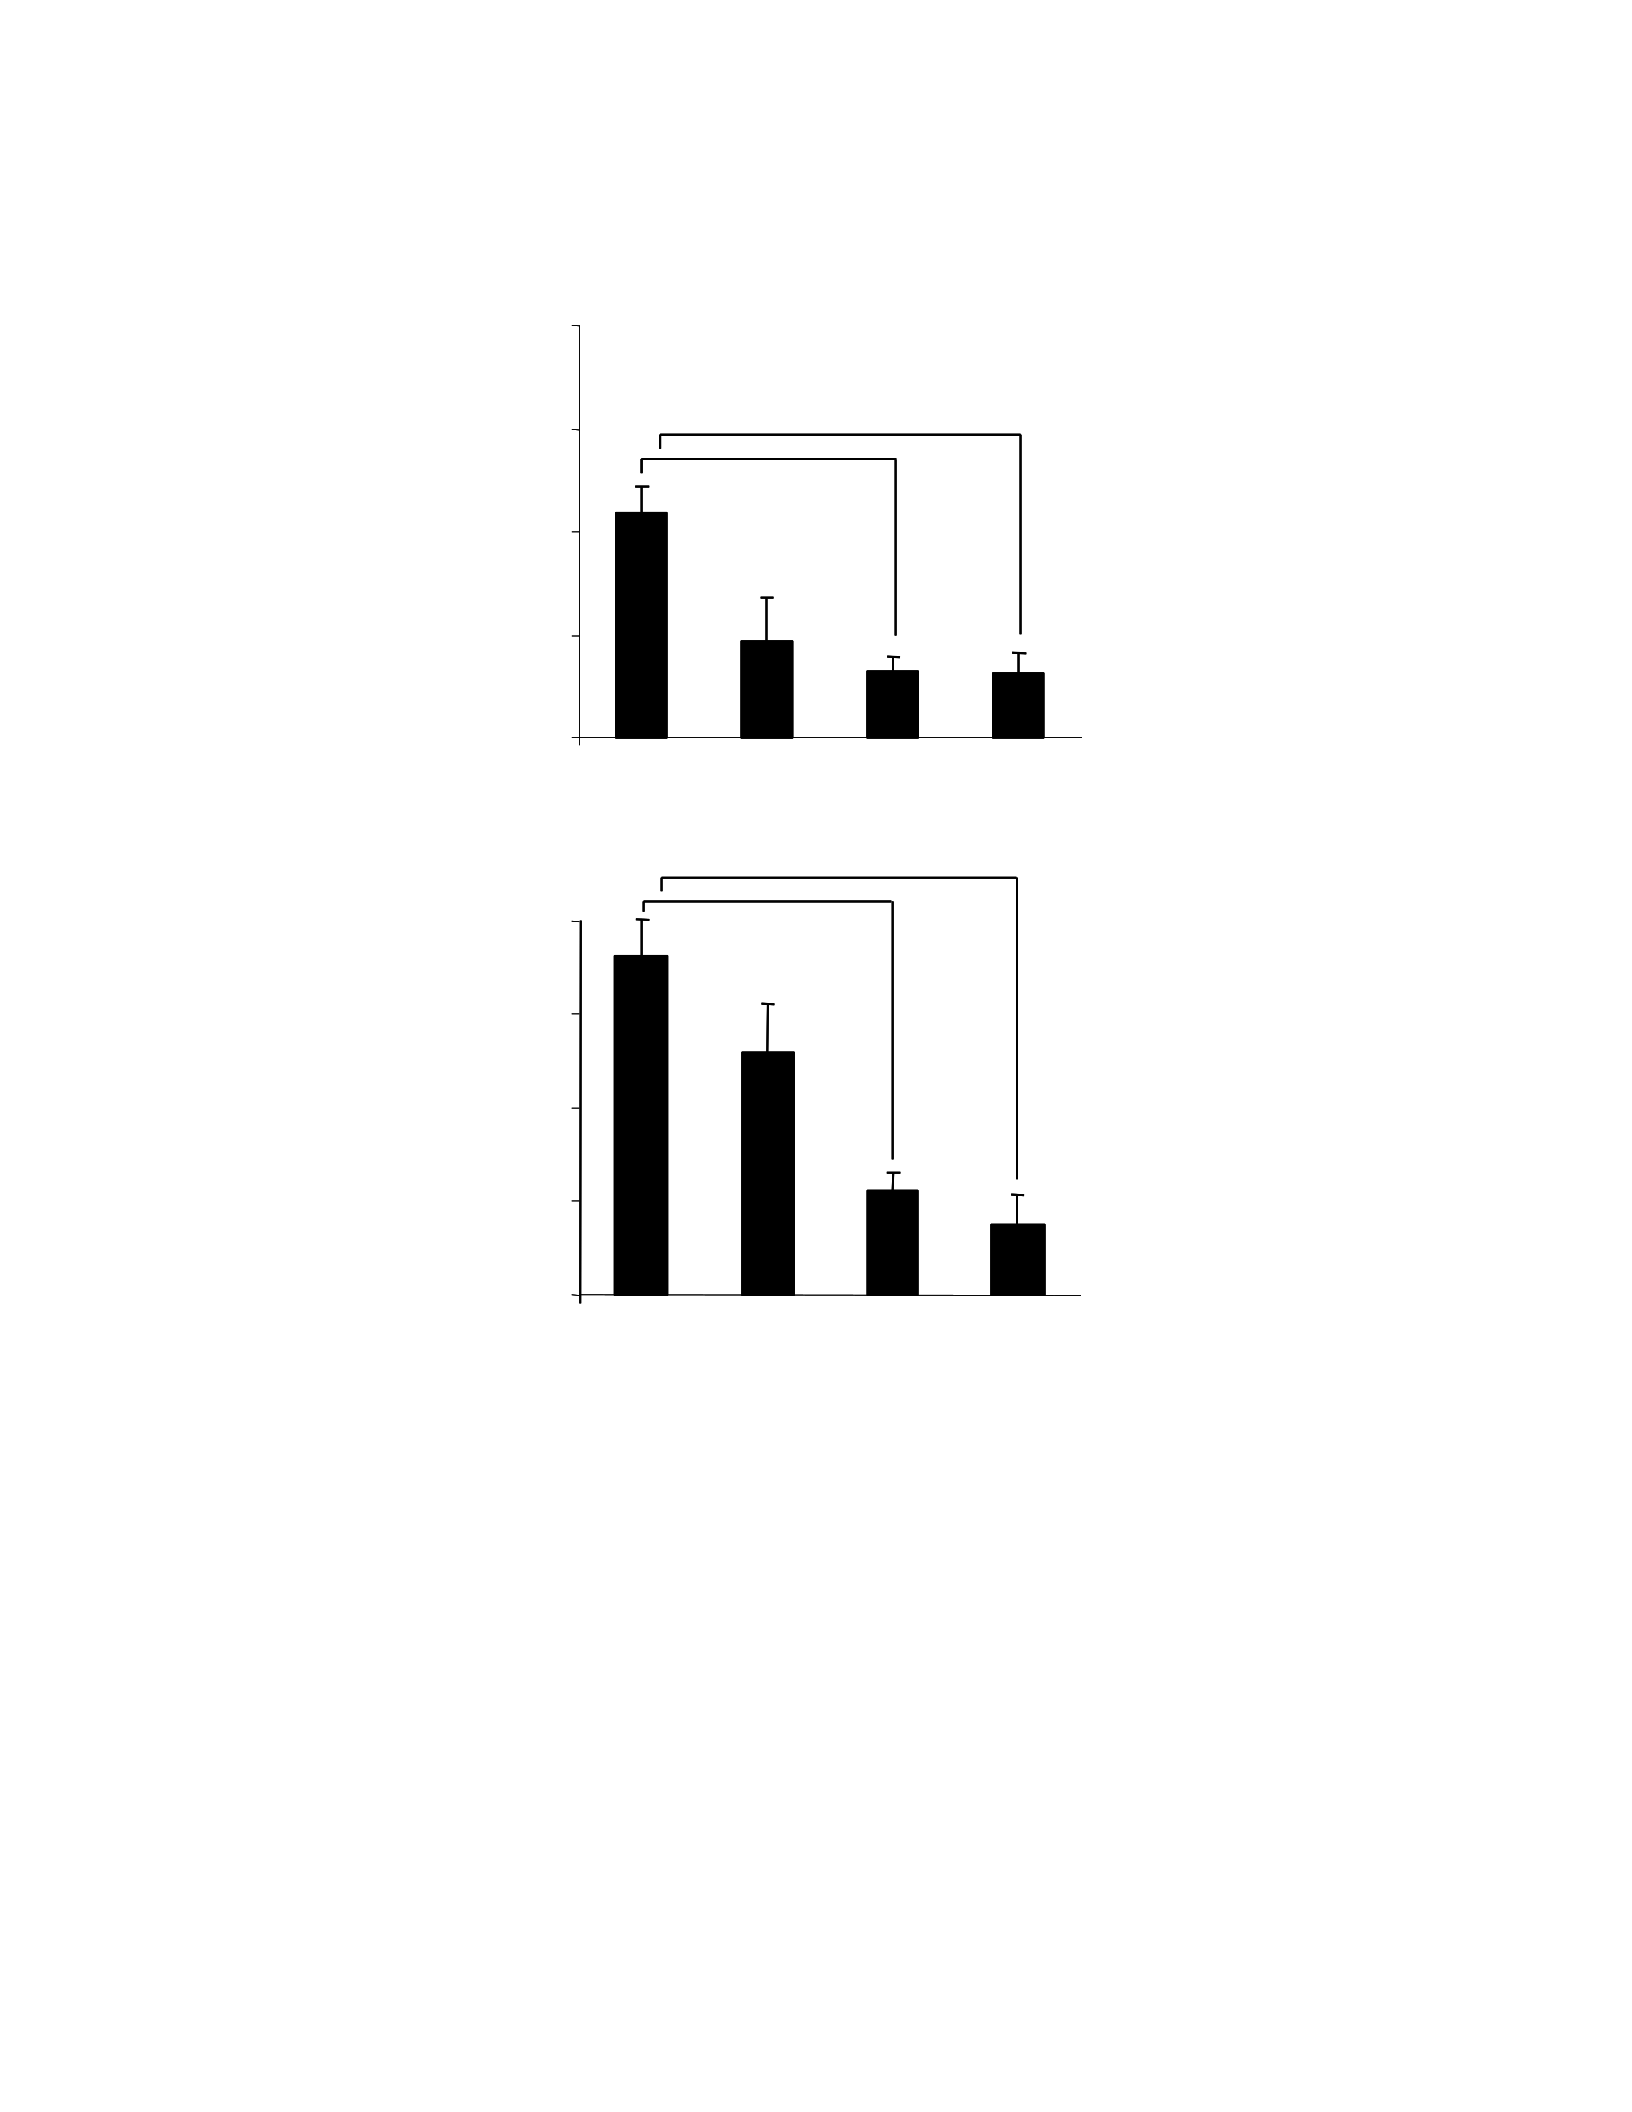
69
a.)
2.0
1.5
1.0
0.5
0
b.)
2.0
Control None Hams Hams &
Quads
1.5
1.0
0.5
0
Control None Hams Hams &
Quads
Figure 4.4. Differences in a.) hamstring fatigability (SlopePTH) and b.) quadriceps fatigability
(SlopePTQ) as represented by the slope among groups characterized by presence of spasticity:
control group, none, hamstring spasticity only (Hams), and hamstring and quadriceps spasticity
(Hams & Quads). * indicates p < 0.01 for post-hoc Tukey HSD pairwise comparisons
**
**
SlopePTH (N·m·rep-1)
SlopePTQ (N·m·rep-1)

70
distinguish between the fatigability of the subjects with CP and the control group, regardless of
muscle group.
The direct relationship of strength and muscle fatigue has been observed in other studies
(Hunter, Critchlow, Shin, & Enoka, 2004; Pincivero, Gear, Sterner, & Karunakara, 2000);
however, the relationship of muscle stiffness and cocontraction to fatigability has not been
previously investigated. An antagonistic relationship of fatigability with cocontraction and
stiffness emerged in the results of the multiple regression analyses. Perhaps this antagonistic
relationship was due to the mechanical effect of cocontraction and stiffness on the net torque
measured by the dynamometer. Cocontraction, as well as stiffness of an antagonistic muscle,
generates opposing joint torque .throughout the range of motion of the agonist. The mechanical
effect of the opposing torque would be a decrease in the net agonist torque. Hamstring
cocontraction, in particular, has been previously shown to cause a significant decrease in the net
moment during knee extension in children with CP (Ikeda, Abel, Granata, & Damiano, 1998).
Therefore, the lower absolute torque level, or weakness, may predispose the smaller decline in
quadriceps PT, and thus, a lesser slope value.
The presence of spasticity was an important factor that explained the differences in
fatigability between the control group and the group with CP. Although there were only 3
subjects without a spastic response in either muscle, there was no significant difference in
SlopePTQ or SlopePTH between this group and the control group. However, there were
significant differences between the control group and the 2 groups with spasticity. The effect
was robust and appeared to be independent of whether spasticity was present in the hamstrings
only or the hamstrings and quadriceps for both SlopePTQ and SlopePTH. Differences between
the spasticity groups were not detected probably due to the fact that we had a group with mixed
quadriceps and hamstrings spasticity rather than a group with isolated quadriceps spasticity.

71
Nevertheless, subjects without spasticity in the group with CP had similar fatigue values as the
control group for both muscle groups.
Surprisingly, the magnitude of spasticity of both the hamstrings (RTH) and quadriceps
(RTQ) was not correlated with either the SlopePTQ or SlopePTH. Perhaps, the small sample
size and range of RT data were not sufficient to achieve a significant correlation. Our data were
comparable to a previous study where RT was calculated at 60 and 120 degrees/second for both
the hamstrings and quadriceps; however, a direct comparison cannot be made between the 2
studies because the RT was normalized by body weight in the previous study (Damiano et al.,
2001). Stiffness values for both the hamstrings and quadriceps in this study were also
comparable to the previous study.
Although the two extremes of stiffness values (Stiff5 and Stiff90) were inversely
correlated with SlopePTQ and SlopePTH, StiffQ30 and StiffQ60 were not correlated with either
fatigue measure. StiffQ5 represents the elastic or intrinsic stiffness of the muscle in the absence
of reflexive activity, whereas stiffness measured at higher velocities is influenced by reflexive
activity for those with spasticity. Because the onset of stretch reflex activity occurred at either 30
or 60 degrees/second in the majority of subjects, we would expect greater variability in StiffQ30
and StiffQ60 in regards to the representation of reflexive stiffness. Furthermore, because of the
velocity dependent nature of reflexive activity, we would expect StiffQ90 to be a more
representative measure of elastic plus reflexive stiffness and StiffQ5 to be more representative of
intrinsic elastic stiffness.
We observed a significant difference in the PT of the quadriceps measured during the
strength test (PTQ) versus the fatigue test (FatPTQ) for the group with CP only. This same
phenomenon was observed in a previous study (Moreau et al., 2006a) and is believed to be of
great clinical importance. During the strength assessment, knee extension always begins from a

72
static position with a 1 minute rest between trials. However, during the fatigue test knee
extension is preceded by a pre-stretch of the muscle (active knee flexion) during subsequent
trials, which may have a potentiation effect on the contractile machinery of the quadriceps. This
enhancement of force production due to pre-stretch has been observed to be significantly greater
in subjects post-stroke compared to healthy subjects during stretch-shortening cycles
(Svantesson, Grimby, & Thomee, 1994). Perhaps force was enhanced in our group of subjects
with CP due to heightened stretch reflex responses or spasticity during pre-stretch of the
quadriceps. For the hamstrings, knee flexion is preceded by pre-stretch (active knee extension)
during all trials of both the strength and fatigue test. The fact that no difference was observed for
the hamstrings between the two measures provides further support for this hypothesis.
Low correlations were observed between the FI and other tested parameters with only
significant correlation between FIH and FIQ observed. Although there was consistency of results
between the FI and the slope, there were more significant correlations for the slope versus the FI.
Despite its popularity of use, the high degree of variability of the FI has been a common finding
(Burdett & Van Swearingen, 1987; Sinacore, Bander, & Delitto, 1994). Greater variability makes
it difficult to detect changes or relationships between variables and could explain the lack of
significance. Furthermore, we have previously shown that the FI is influenced greatly by the
maximum torque value, FI (PT/Max PT)*100% (Moreau et al., 2006b). Therefore, it appears
that the slope is a more sensitive measure of muscle fatigability than the FI.
It is important to note that other factors, beyond the scope of this study, such as energy
metabolism, morphological differences, patterns of motor unit recruitment, and voluntary
activation may play a role in the differences in fatigability between the two groups. Future
studies are needed to decipher the influence of these variables on the level of fatigability. Lastly,
caution should be used in extrapolating the results of this study to muscle groups other than the

73
knee flexors and extensors, as muscle characteristics such as size, fiber type distribution, fiber
arrangement, recruitment, and rate coding strategies differ considerably across muscle groups.
In conclusion, the results of this study suggest that the maximum absolute torque level
played a significant role in the fatigue resistance observed in the group with CP. The opposing
torque created by cocontraction of the hamstrings, which was inversely related to quadriceps
fatigability, and the opposing torque generated by intrinsic stiffness of the quadriceps, which was
inversely related to hamstring fatigability, possibly contributed to the lower net agonist torque
level. Furthermore, the presence of spasticity, regardless of muscle group, was related to lower
levels of fatigability compared to control subjects without motor disability.
Reference List
Baratta, R., Solomonow, M., Zhou, B. H., Letson, D., Chuinard, R., & D'Ambrosia, R. (1988).
Muscular coactivation. The role of the antagonist musculature in maintaining knee
stability. Am.J.Sports Med., 16, 113-122.
Barnes, W. S. (1980). The relationship between maximum isometric strength and intramuscular
circulatory occlusion. Ergonomics, 23, 351-357.
Bigland-Ritchie, B., Johansson, R., Lippold, O. C., & Woods, J. J. (1983). Contractile speed and
EMG changes during fatigue of sustained maximal voluntary contractions.
J.Neurophysiol., 50, 313-324.
Booth, C. M., Cortina-Borja, M. J., & Theologis, T. N. (2001). Collagen accumulation in
muscles of children with cerebral palsy and correlation with severity of
spasticity. Dev.Med.Child Neurol., 43, 314-320.
Burdett, R. G. & Van Swearingen, J. (1987). Reliability of isokinetic muscle endurance tests.
The Journal of Orthopaedic and Sports Physical Therapy, 8, 484-488.
Burke, R. E., Levine, D. N., Tsairis, P., & Zajac, F. E. (1973). Physiological types and
histochemical profiles in motor units of the cat gastrocnemius. Journal of Physiology
(London), 234, 723-748.
Castle, M. E., Reyman, T. A., & Schneider, M. (1979). Pathology of spastic muscle in cerebral
palsy. Clin.Orthop.Relat Res., 223-232.
Damiano, D. L., Quinlivan, J., Owen, B. F., Shaffrey, M., & Abel, M. F. (2001). Spasticity
versus strength in cerebral palsy: relationships among involuntary resistance, voluntary
torque, and motor function. Eur.J.Neurol., 8 Suppl 5, 40-49.

74
Damiano, D. L., Quinlivan, J. M., Owen, B. F., Payne, P., Nelson, K. C., & Abel, M. F. (2002).
What does the Ashworth scale really measure and are instrumented measures more valid
and precise? Dev.Med.Child Neurol., 44, 112-118.
Friden, J. & Lieber, R. L. (2003). Spastic muscle cells are shorter and stiffer than normal cells.
Muscle Nerve, 27, 157-164.
Hufschmidt, A. & Mauritz, K. H. (1985). Chronic transformation of muscle in spasticity: a
peripheral contribution to increased tone. J.Neurol.Neurosurg.Psychiatry, 48, 676-685.
Hunter, S. K., Critchlow, A., Shin, I. S., & Enoka, R. M. (2004). Fatigability of the elbow flexor
muscles for a sustained submaximal contraction is similar in men and women matched
for strength. J Appl.Physiol, 96, 195-202.
Hunter, S. K. & Enoka, R. M. (2001). Sex differences in the fatigability of arm muscles depends
on absolute force during isometric contractions. J Appl.Physiol, 91, 2686-2694.
Ikeda, A. J., Abel, M. F., Granata, K. P., & Damiano, D. L. (1998). Quantification of
cocontraction in spastic cerebral palsy. Electromyogr.Clin.Neurophysiol., 38, 497-504.
Ito, J., Araki, A., Tanaka, H., Tasaki, T., Cho, K., & Yamazaki, R. (1996). Muscle
histopathology in spastic cerebral palsy. Brain Dev., 18, 299-303.
Kanehisa, H., Okuyama, H., Ikegawa, S., & Fukunaga, T. (1995). Fatigability during repetitive
maximal knee extensions in 14-year-old boys. Eur.J Appl.Physiol Occup.Physiol, 72,
170-174.
Lamontagne, A., Malouin, F., & Richards, C. L. (2000). Contribution of passive stiffness to
ankle plantarflexor moment during gait after stroke. Arch.Phys.Med.Rehabil., 81, 351-
358.
Lance, J. W. (1980). Symposium synopsis. In R.G.Feldman, R. R. Young, & W. P. Koella
(Eds.), Spasticity: Disordered motor control (pp. 485-500). Chicago: Yearbook Medical
Publishers.
Lanza, I. R., Russ, D. W., & Kent-Braun, J. A. (2004). Age-related enhancement of fatigue
resistance is evident in men during both isometric and dynamic tasks. J Appl.Physiol, 97,
967-975.
Lee, H. M., Huang, Y. Z., Chen, J. J., & Hwang, I. S. (2002). Quantitative analysis of the
velocity related pathophysiology of spasticity and rigidity in the elbow flexors. J
Neurol.Neurosurg.Psychiatry, 72, 621-629.
Lehmann, J. F., Price, R., deLateur, B. J., Hinderer, S., & Traynor, C. (1989). Spasticity:
quantitative measurements as a basis for assessing effectiveness of therapeutic
intervention. Arch.Phys.Med Rehabil., 70, 6-15.
Lenman, A. J., Tulley, F. M., Vrbova, G., Dimitrijevic, M. R., & Towle, J. A. (1989). Muscle
fatigue in some neurological disorders. Muscle Nerve, 12, 938-942.

75
Lieber, R. L., Steinman, S., Barash, I. A., & Chambers, H. (2004). Structural and functional
changes in spastic skeletal muscle. Muscle Nerve, 29, 615-627.
Marbini, A., Ferrari, A., Cioni, G., Bellanova, M. F., Fusco, C., & Gemignani, F. (2002).
Immunohistochemical study of muscle biopsy in children with cerebral palsy. Brain
Dev., 24, 63-66.
Miller, R. G., Green, A. T., Moussavi, R. S., Carson, P. J., & Weiner, M. W. (1990). Excessive
muscular fatigue in patients with spastic paraparesis. Neurology, 40, 1271-1274.
Milner, T. E., Cloutier, C., Leger, A. B., & Franklin, D. W. (1995). Inability to activate muscles
maximally during cocontraction and the effect on joint stiffness. Exp.Brain Res., 107,
293-305.
Moreau, N. G., Li, L., & Damiano, D. L. (2006a). A feasible and reliable muscle fatigue protocol
for individuals with cerebral palsy. Manuscript submitted for publication.
Moreau, N. G., Li, L., & Damiano, D. L. (2006b). Are muscles more fatigable in individuals
with cerebral palsy? Unpublished manuscript.
Pincivero, D. M., Gandaio, C. M., & Ito, Y. (2003). Gender-specific knee extensor torque, flexor
torque, and muscle fatigue responses during maximal effort contractions.
Eur.J.Appl.Physiol, 89, 134-141.
Pincivero, D. M., Gear, W. S., & Sterner, R. L. (2001). Assessment of the reliability of high-
intensity quadriceps femoris muscle fatigue. Med.Sci.Sports Exerc., 33, 334-338.
Pincivero, D. M., Gear, W. S., Sterner, R. L., & Karunakara, R. G. (2000). Gender differences in
the relationship between quadriceps work and fatigue during high-intensity exercise.
Journal of Strength and Conditioning Research, 14, 202-206.
Ratel, S., Lazaar, N., Williams, C. A., Bedu, M., & Duche, P. (2003). Age differences in human
skeletal muscle fatigue during high-intensity intermittent exercise. Acta Paediatr., 92,
1248-1254.
Romanini, L., Villani, C., Meloni, C., & Calvisi, V. (1989). Histological and morphological
aspects of muscle in infantile cerebral palsy. Ital.J.Orthop.Traumatol., 15, 87-93.
Rose, J., Haskell, W. L., Gamble, J. G., Hamilton, R. L., Brown, D. A., & Rinsky, L. (1994).
Muscle pathology and clinical measures of disability in children with cerebral palsy.
J.Orthop.Res., 12, 758-768.
Sinacore, D. R., Bander, B. L., & Delitto, A. (1994). Recovery from a 1-minute bout of fatiguing
exercise: characteristics, reliability, and responsiveness. Phys.Ther., 74, 234-241.
Svantesson, U., Grimby, G., & Thomee, R. (1994). Potentiation of concentric plantar flexion
torque following eccentric and isometric muscle actions. Acta Physiol Scand., 152, 287-
293.

76
Svantesson, U. & Sunnerhagen, K. S. (1997). Stretch-shortening cycle in patients with upper
motor neuron lesions due to stroke. Eur.J.Appl.Physiol Occup.Physiol, 75, 312-318.
Thorstensson, A. & Karlsson, J. (1976). Fatiguability and fibre composition of human skeletal
muscle. Acta Physiol Scand., 98, 318-322.
Tyler, A. E. & Hutton, R. S. (1986). Was Sherrington right about co-contractions? Brain Res.,
370, 171-175.
Weir, J. P., Keefe, D. A., Eaton, J. F., Augustine, R. T., & Tobin, D. M. (1998). Effect of fatigue
on hamstring coactivation during isokinetic knee extensions. Eur.J Appl.Physiol
Occup.Physiol, 78, 555-559.

77
CHAPTER 5: GENERAL DISCUSSION
Summary of Results
Fatigue is a frequent subjective complaint in individuals with cerebral palsy (CP) and has
been cited as a cause of worsening disability in adulthood (Bottos, Feliciangeli, Sciuto, Gericke,
& Vianello, 2001; Jahnsen, Villien, Egeland, Stanghelle, & Holm, 2004). Previous work on
fatigue in people with CP has focused primarily on the cardiorespiratory system. This approach
has led to limited success as most authors agree that local muscle factors, such as muscle fatigue
are responsible for the lower VO2max and limitations in activity (Hoofwijk, Unnithan, & Bar-Or,
1995; Rose, Haskell, & Gamble, 1993; Unnithan, Dowling, Frost, & Bar-Or, 1996). Therefore,
the purpose of the experiments presented in Chapters 2, 3, and 4 was to further the measurement
and understanding of muscle fatigue in the CP population utilizing the WHO ICF (2001) model
as a conceptual framework. Based on this model, the measurement of muscle fatigue at the body
function level, the relationship of fatigue to activities and participation, and the possible
contributing factors to fatigue at the body function level were investigated.
In Chapter 2, an isokinetic muscle fatigue protocol consisting of the performance of 35
consecutive knee flexion and extension repetitions at 60 degrees/second was determined to be
feasible for mild to moderately impaired subjects with CP over a wide age range. Furthermore,
two established measures of muscle fatigability (fatigue index and rate of decline in peak torque)
were reliably measured from the muscle fatigue protocol. In Chapter 3, the muscle fatigability of
the hamstrings and quadriceps in individuals with CP were compared to a control group of age-
matched peers without CP. Contrary to our original hypothesis, the hamstrings and quadriceps in
individuals with CP were observed to be less fatigable than in age-matched peers without motor
disability. Furthermore, lower levels of function, participation, and walking velocity were
associated with lower levels of muscle fatigability in the group with CP. In Chapter 4, it was

78
hypothesized that other impairments at the body function level, such as weakness, spasticity,
stiffness, and cocontraction, may contribute to the fatigue resistance observed in the subjects
with CP. Results indicate that hamstring strength and antagonistic quadriceps stiffness were the
strongest predictors of hamstring fatigability, while cocontraction of the hamstrings was the
strongest predictor of quadriceps fatigability. Furthermore, the level of fatigability in subjects
with CP who did not have spasticity did not differ from the control subjects, indicating that
spasticity may play a role in the fatigue resistance observed in this population.
Discussion of Results and Future Studies
The 3 main findings from these experiments are the following 1.) Muscle fatigue of the
hamstrings and quadriceps can be reliably measured in mild to moderately involved individuals
with CP utilizing an isokinetic protocol; 2.) The hamstrings and quadriceps of individuals with
CP are less fatigable than those of age-matched peers without motor disability, and the lower
levels of fatigability are inversely related to measures of function and participation; and 3.) The
fatigue resistance observed in the hamstrings and quadriceps of individuals with CP is related to
weakness, spasticity, stiffness, and cocontraction of the muscles in question.
Muscle fatigue has been investigated in healthy adults as well as in other neurological
populations, such as multiple sclerosis, stroke, and spinal cord injury that present with spasticity
and other similar impairments to those seen in CP. Although subjective complaints of fatigue
have been documented in people with CP, muscle fatigue has been overlooked in the assessment
of muscle performance. Therefore, it was critical to establish a feasible and reliable assessment
of muscle fatigue in this population. First, it was necessary to define muscle fatigue before
establishing a measurement protocol. Muscle fatigue, or fatigability, was defined as a reduction
in the force-generating capacity of the neuromuscular system that occurs during sustained
activity (Bigland-Ritchie, Johansson, Lippold, & Woods, 1983). Based on this definition, an

79
isokinetic muscle fatigue protocol was tested in people with CP over 10 years of age. This
protocol was observed to be reliable in mild to moderately impaired children and young adults.
Based on this protocol, the results of the 2nd and 3rd experiments indicate that stronger,
more functional people with and without CP have higher levels of muscle fatigability of the
hamstrings and quadriceps compared to those with CP who are weaker and less functional. These
results do not imply that the muscles of people with CP are somehow superior to those without
disability due to the observed fatigue-resistance. Rather, the results suggest that a certain level of
muscle fatigability, as measured by the slope and FI, is typical of a normally developed muscle.
So how do we explain that the knee muscles of people with CP are less fatigable that those
without motor disability? Results suggest a discernable relationship of agonist and antagonistic
forces with muscle fatigability. An agonist relationship of hamstring strength and an antagonistic
relationship of quadriceps stiffness to hamstring fatigability were observed. Similarly, an
antagonistic relationship of hamstrings cocontraction with quadriceps fatigability was observed.
The positive relationship between the strength of an agonist muscle and the fatigability of that
muscle has shown by others and is thought to be the result of muscle mass differences.
According to the muscle mass or strength hypothesis, stronger subjects have more blood flow
occlusion than weaker subjects at the same relative load, resulting in greater fatigability (Barnes,
1980). Others believe that the higher absolute torque level predisposes the muscle to a greater
rate of decline (Pincivero, Gandaio, & Ito, 2003). This may be due to a greater proportion of
type II, fast, fatigable fibers, which are typical of stronger muscles (Miller, MacDougall,
Tarnopolsky, & Sale, 1993). The inverse relationship between antagonistic stiffness and
cocontraction with fatigability, however, has not been investigated previously. We have
proposed a mechanical hypothesis to explain this relationship. According to this hypothesis,
antagonistic stiffness and cocontraction would generate opposing torque throughout the range of

80
motion of the agonist. Because cocontraction and stiffness are inherently higher in this
population, the amount of agonist torque negated by these opposing forces would be substantial.
This would result in a lower measured (net) torque level, hence weakness. Weakness would
further predispose the muscle to be less fatigable.
Theoretically, to assess the effect of strength on the level of fatigability, we would need
to match subjects with and without CP for strength for comparison between groups (Hunter,
Critchlow, Shin, & Enoka, 2004). Realistically, this would not be feasible, as in our study alone
we found strength differences as high as 60% between groups. Perhaps, an alternative would be
to investigate the differences between the groups with a measure of fatigue that is not dependent
on the maximum torque level. The FI and the slope are both proportional to the difference
between the highest and lowest torque, which can be influenced by the maximum torque. The FI
is further inversely proportional to the maximum torque level, as observed in Chapter 4.
However, Sinacore, Bander, and Delitto (1994) showed that recovery of peak torque of the
quadriceps after completion of a fatigue protocol is a reliable measure that is not dependent on
the maximum torque level. Furthermore, the measure was responsive to 12 weeks of endurance
training, whereas the percentage decline in peak torque (FI) was not altered as a result of
training. Future studies should investigate the differences in recovery of peak torque between
subjects with and without CP after completion of the fatigue protocol described in Chapter 2 to
see if the differences in fatigability persist. The results of this study should provide further
insight into the influence of maximum torque level, or strength, on the level of muscle
fatigability.
In order to further explore the relationship between cocontraction and fatigability, future
studies should investigate the relative contribution of antagonist muscle activity to the net
moment measured throughout the fatigue protocol. For example, if both agonist and antagonist

81
force production decline at similar rates during the fatigue protocol for subjects with CP, then the
torque output should remain relatively constant throughout the protocol due to the reduced
contribution of the antagonist. This would result in a small rate of decline in PT and hence, a low
rate of fatigability as measured by the slope. The results of this study would provide direct
evidence of the contribution of antagonist cocontraction to the rate of decline in peak torque of
the agonist muscle. Figure 5.1 illustrates a hypothetical situation where the rate of decline (slope)
of agonist torque is identical for the groups with and without CP, but the magnitude of torque
output is substantially lower for the group with CP secondary to weakness. The contribution of
antagonist force production to the net torque remains constant for the control group, as has been
observed by Kellis (2003) in healthy subjects. In contrast, the magnitude of antagonist force
production and rate of decline is much greater for the group with CP. Therefore, the result is a
substantially lower net torque output and a lower rate of decline for the group with CP, similar to
the results of our experiments.
The presence of spasticity, regardless of muscle group, was also a contributing factor to
the lower muscle fatigability observed in the subjects with CP. The fatigability of the subjects in
the CP group without spasticity did not differ from the control subjects. Only those subjects with
spasticity of either muscle group had lower levels of fatigability compared to controls. This
result provides indirect support that spasticity results in alterations of muscle properties that may
include fiber type changes that would predispose the muscles to a lower rate of fatigue.
Future studies are needed in order to address the effects of spasticity on fiber type
composition and the resultant effect on the level of muscle fatigability observed in this
population. An issue that has not been addressed in these biopsy studies of spastic muscle is the
presence and amount of spasticity, if any, in the muscles sampled. Both clinically and
experimentally, it is common to have spasticity in certain muscle groups and not in others
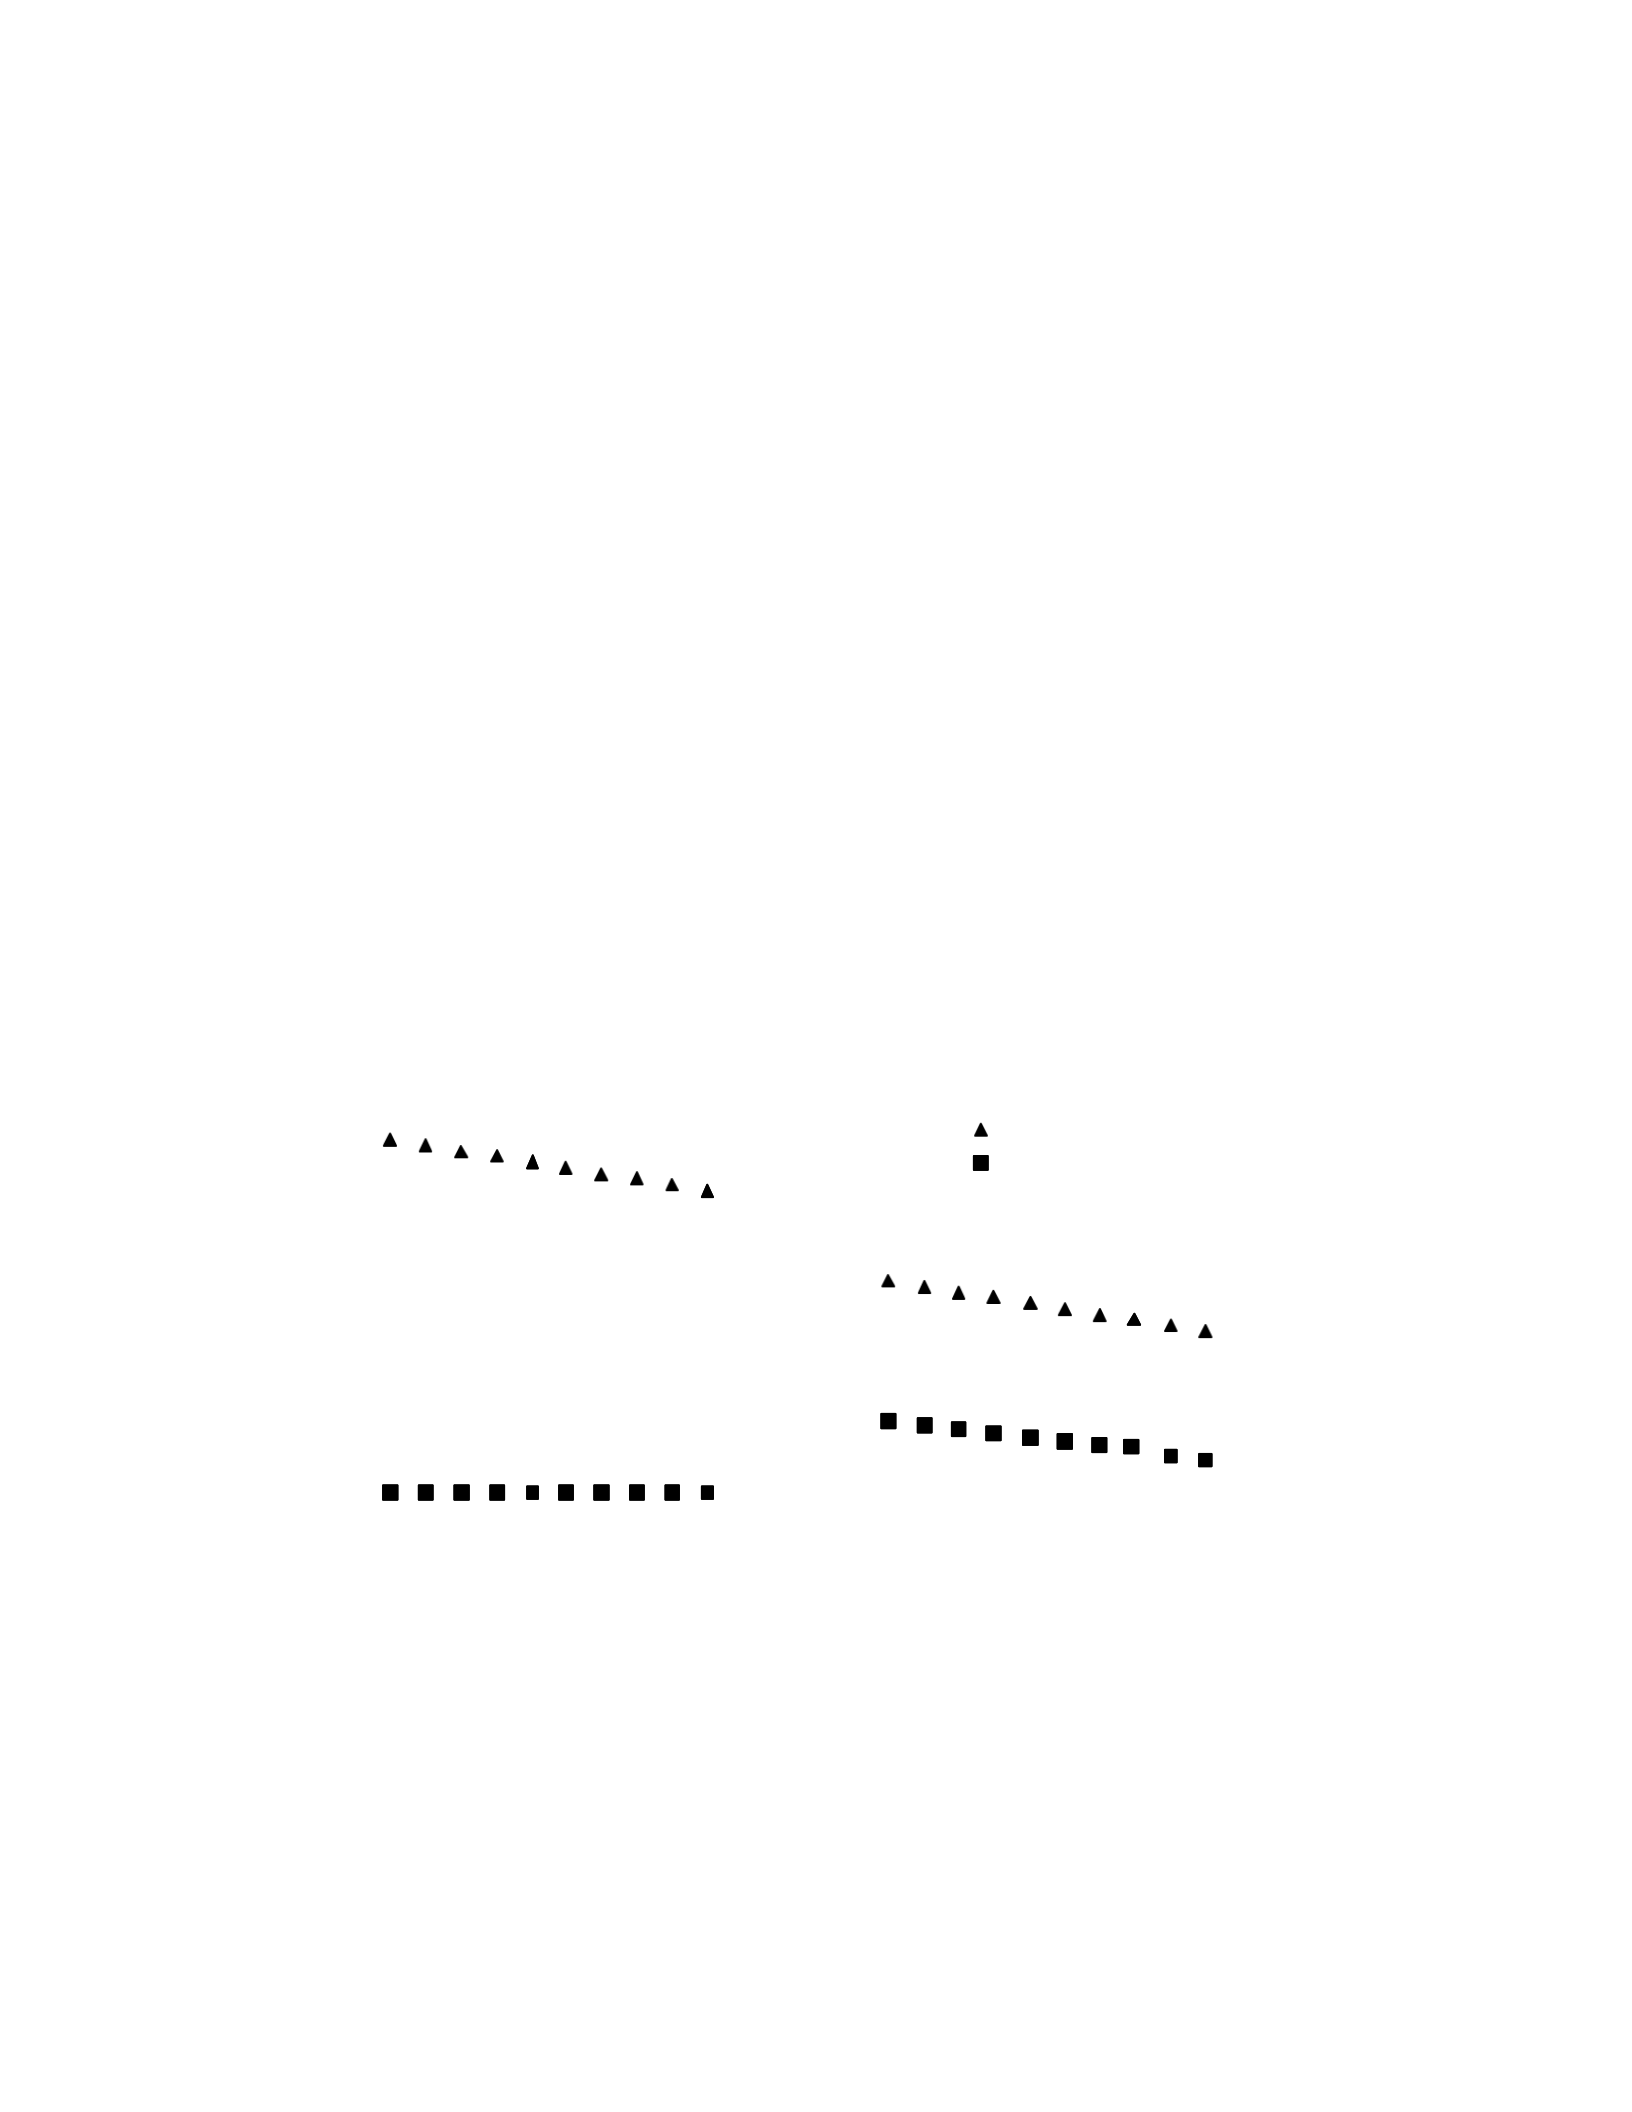
b = 2.0
Agonist torque
Antagonist
torque Net
Torque
b = 2.0
b = 2.0
b = 0
b = 0.5
b = 1.5
82
(Damiano et al., 2002; Katz, Rovai, Brait, & Rymer, 1992). For example, it is more common to
have spasticity of the hamstrings than in the quadriceps. However, the relationship of fiber type
to the amount of spasticity has not been explored. Therefore, if spasticity is believed to result in
secondary myopathic changes, the presence and degree of spasticity should be documented for
the muscles in question. Until this is documented and investigated experimentally, we cannot
accurately say that these findings are representative of “spastic” muscle. Future studies should
include biopsies of identical muscles across individuals with EMG verification of the presence
of spasticity of each muscle. Fiber type compositions could then be compared to investigate
whether or not the relationship exists. The results of this study would shed considerable light on
the effect of spasticity on muscle fiber type composition and the resulting effect on muscle
performance.
150
100
50
0
Control Cerebral Palsy
Figure 5.1. Hypothetical example of agonist and antagonist contributions to the net joint torque,
represented by a straight line, over 10 consecutive repetitions for a control group and a group
with CP. The effect on the rate of the decline in peak torque is represented by the absolute value
of the slope (b).
Torque (N·m)

83
Clinical Significance
Although previous research has focused on the amelioration of spasticity as a primary
goal of treatment, current research has shown that other aspects of muscle performance, such as
strength, have higher correlations with gross motor function and walking velocity, and are
amenable to treatment. Therefore, most studies of muscle function in people with CP have
focused on lower extremity strength, thereby overlooking muscle fatigue as an important
component of muscle function. A search of the medical literature revealed there are no
established muscle fatigue protocols for people with CP. Therefore, this is the first investigation
of localized muscle fatigue in this population by means of voluntary contraction in conjunction
with measures of strength, hypertonia, and function. The establishment of a feasible and reliable
muscle fatigue protocol in this population has widespread applications for future research as
well as for clinical assessment.
The WHO ICF model was developed as a framework to assist in the understanding and
measurement of health outcomes. By investigating muscle fatigue at the body function level, as
well as the level of functioning of the individual (activities) and the whole person in a social
context (participation), we have provided a more comprehensive view of muscle fatigue. For
example, this series of experiments has provided unique insight into the muscle fatigue
characteristics of this population and the relationship to function. For example, based on the
results of our study, a clinician would expect muscle fatigue to increase, not decrease, as walking
velocity and strength improved as the result of an intervention program in a person with CP. This
runs counter-intuitive to the view that increased muscle fatigue is a negative symptom that would
occur in lower functioning patients. Based on our definition and measurement of fatigue, the
results of our study challenge the notion that less fatigable is better in this population. It raises

84
the question of whether the fatigue resistance observed in this population is the product of
disordered motor control and possibly, muscle property alterations.
Traditionally, muscle fatigue was thought to occur exclusively either in the central
nervous system or the peripheral nervous system. However, since muscle activity depends on
the integrity of the entire chain of events, muscle fatigue may occur at central and peripheral
sites simultaneously (McComas, Miller, & Gandevia, 1995). Thus, muscle fatigue should be
viewed as the result of the interaction of several different processes in both the central and
peripheral nervous system. This series of experiments provides a unique contribution to the
literature, thereby supporting the interaction of the central and peripheral nervous system in the
process of muscle fatigue induced by voluntary muscle contractions in people with CP.
Lastly, these results provide a better understanding of the possible contributing factors to
fatigue resistance, improving our understanding of muscle fatigue in this population. In addition,
the results have increased our understanding of the complex interrelationships among
impairments in CP, such as strength, cocontraction, spasticity, and stiffness. The results of this
study open the door for further exploration into this area of study and the possible muscle
adaptations that may occur secondary to CP.
Reference List
Barnes, W. S. (1980). The relationship between maximum isometric strength and intramuscular
circulatory occlusion. Ergonomics, 23, 351-357.
Bigland-Ritchie, B., Johansson, R., Lippold, O. C., & Woods, J. J. (1983). Contractile speed and
EMG changes during fatigue of sustained maximal voluntary contractions.
J.Neurophysiol., 50, 313-324.
Bottos, M., Feliciangeli, A., Sciuto, L., Gericke, C., & Vianello, A. (2001). Functional status of
adults with cerebral palsy and implications for treatment of children. Dev.Med.Child
Neurol., 43, 516-528.
Damiano, D. L., Quinlivan, J. M., Owen, B. F., Payne, P., Nelson, K. C., & Abel, M. F. (2002).
What does the Ashworth scale really measure and are instrumented measures more valid
and precise? Dev.Med.Child Neurol., 44, 112-118.

85
Hoofwijk, M., Unnithan, V., & Bar-Or, O. (1995). Maximal treadmill performance of children
with cerebral palsy. Pediatric Exercise Science, 7, 305-313.
Hunter, S. K., Critchlow, A., Shin, I. S., & Enoka, R. M. (2004). Fatigability of the elbow flexor
muscles for a sustained submaximal contraction is similar in men and women matched
for strength. J Appl.Physiol, 96, 195-202.
Jahnsen, R., Villien, L., Egeland, T., Stanghelle, J. K., & Holm, I. (2004). Locomotion skills in
adults with cerebral palsy. Clin.Rehabil., 18, 309-316.
Katz, R. T., Rovai, G. P., Brait, C., & Rymer, W. Z. (1992). Objective quantification of spastic
hypertonia: correlation with clinical findings. Arch.Phys.Med.Rehabil., 73, 339-347.
Kellis, E. (2003). Antagonist moment of force during maximal knee extension in pubertal boys:
effects of quadriceps fatigue. European Journal of Applied Physiology, 89, 271-280.
McComas, A. J., Miller, R. G., & Gandevia, S. C. (1995). Fatigue brought on by malfunction of
the central and peripheral nervous systems. Adv.Exp.Med.Biol., 384, 495-512.
Miller, A. E., MacDougall, J. D., Tarnopolsky, M. A., & Sale, D. G. (1993). Gender differences
in strength and muscle fiber characteristics. Eur.J Appl.Physiol Occup.Physiol, 66, 254-
262.
Pincivero, D. M., Gandaio, C. M., & Ito, Y. (2003). Gender-specific knee extensor torque, flexor
torque, and muscle fatigue responses during maximal effort contractions.
Eur.J.Appl.Physiol, 89, 134-141.
Rose, J., Haskell, W. L., & Gamble, J. G. (1993). A comparison of oxygen pulse and respiratory
exchange ratio in cerebral palsied and nondisabled children. Arch.Phys.Med.Rehabil., 74,
702-705.
Sinacore, D. R., Bander, B. L., & Delitto, A. (1994). Recovery from a 1-minute bout of fatiguing
exercise: characteristics, reliability, and responsiveness. Phys.Ther., 74, 234-241.
Unnithan, V. B., Dowling, J. J., Frost, G., & Bar-Or, O. (1996). Role of cocontraction in the O2
cost of walking in children with cerebral palsy. Med.Sci.Sports Exerc., 28, 1498-1504.

Body Functions are physiological functions of body systems (including
psychological functions).
Body Structures are anatomical parts of the body such as organs, limbs and
their components.
Impairments are problems in body function or structure such as a
significant deviation or loss.
Activity is the execution of a task or action by an individual.
Participation is involvement in a life situation.
Activity Limitations are difficulties an individual may have in executing
activities.
Participation Restrictions are problems an individual may experience in
involvement in life situations.
Environmental Factors
environment in which people live and conduct their lives
.
86
APPENDIX 1: EXPANDED LITERATURE REVIEW
Introduction
This review is designed to build a foundation for understanding muscle fatigue in
Cerebral Palsy (CP) and its potential role in the disablement process. The relationships between
muscle fatigue and other impairments will be explored, as well as how fatigue, in general, has
been shown to impact activity, participation, and quality of life. The World Health
Organization’s International Classification of Functioning, Disability and Health (ICF) will be
used as a framework to illustrate this process (Figure A.1) (World Health Organization, 2001).
The formal definitions of the ICF are provided in Table A.1.
Table A.1
WHO ICF Model Definitions
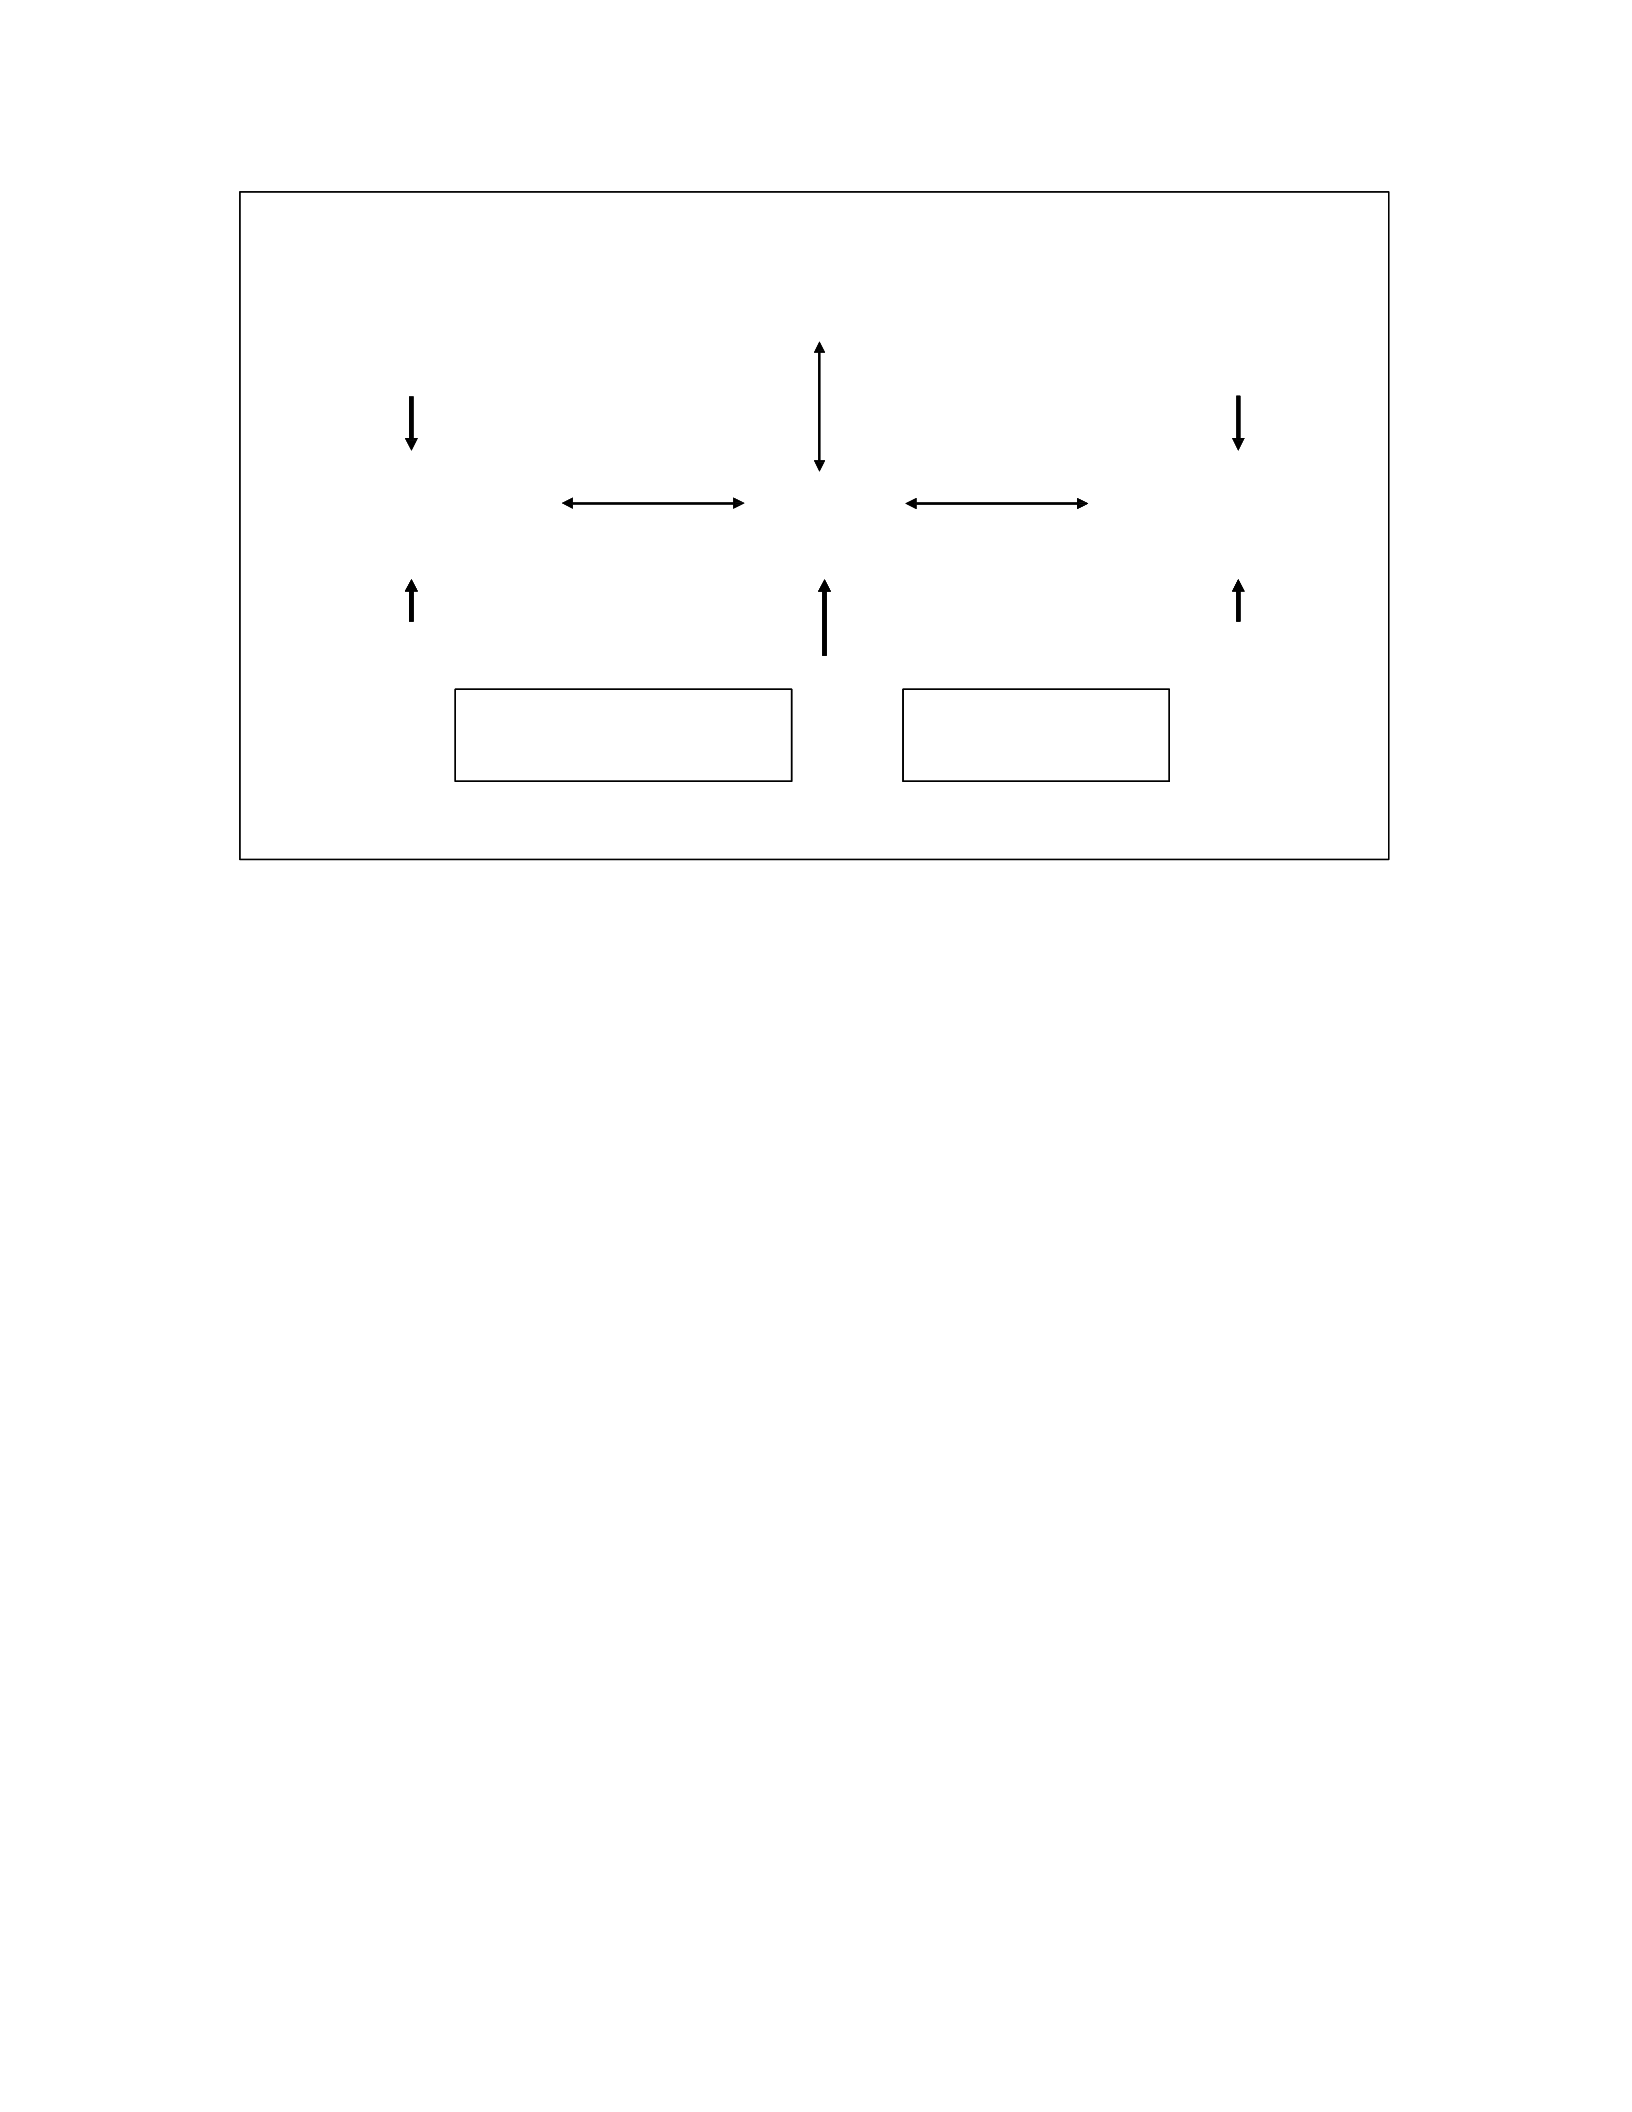
87
Figure A.1. The World Health Organization’s International Classification of
Functioning, Disability and Health (ICF, 2001)
CP describes a collection of disorders “of the development of movement and posture,
causing activity limitation, that are attributed to non-progressive disturbances that occurred in
the developing fetal or infant brain” (Bax et al., 2005). CP is not a disease, per se, but rather, a
descriptive term that describes a heterogeneous group of children who often manifest with
chronic motor impairment. Although variability exists with respect to the degree of impairments
individuals with CP may exhibit, common impairments include loss of selective motor control,
spasticity, muscle weakness, co-contraction, and contractures. In turn, these impairments can
lead to activity restrictions such as difficulty in walking and other activities of daily living, often
leading to worsening disability throughout the lifespan.
Studies over the last fifteen years have documented a gradual onset of newly recognized
problems in adults with CP, such as fatigue, musculoskeletal pain, and deterioration of functional
skills (Andersson & Mattsson, 2001; Bottos, Feliciangeli, Sciuto, Gericke, & Vianello, 2001;
Health condition
(disorder or
disease)
Body structures
and functions
Activity Participation
Environment
al
Factors
Persona
l
Factors

88
Cathels & Reddihough, 1993; Gajdosik & Cicirello, 2001; Jahnsen, Villien, Aamodt, Stanghelle,
& Holm, 2004; Jahnsen, Villien, Egeland, Stanghelle, & Holm, 2004; Jahnsen, Villien,
Stanghelle, & Holm, 2003; Murphy, Molnar, & Lankasky, 1995; Pimm, 1992). These problems
manifest in adolescence and early adulthood and have consequences for activities and
participation in work and social situations. Furthermore, these studies provide evidence of the
progression of certain impairments in CP and the need for targeted interventions throughout the
life span, despite the non-progressive brain lesion (Figure A.2).
Physical fatigue, in particular, has been identified as a significant impairment in adults
with CP compared with the general population and has been significantly associated with
deterioration of functional skills, bodily pain, limitations in physical and emotion role function,
and low life satisfaction (Jahnsen et al., 2003) (Figure A.2). In fact, adults with CP report fatigue
as a main cause of the deterioration or cessation of their walking ability (Bottos et al., 2001;
Jahnsen et al., 2004; Murphy et al., 1995). Murphy et al. (1995) reported that 75% of subjects
ceased to walk by the age of 25 due to fatigue and inefficiency of ambulation. Jahnsen et al.
(2004) reported that 44% of subjects had deterioration of walking due to fatigue, pain, and lack
of adapted physical activity. However, fatigue was assessed subjectively in these studies through
the use of questionnaires and interviews.
The term “fatigue” has been subjectively used to describe a multitude of mental and
physical symptoms and is often confused with other symptoms, such as weakness (Schwid,
Covington, Segal, & Goodman, 2002). Therefore, these self-report questionnaires may not be
adequate in the assessment of fatigue. Jahnsen et al. (2003) was the only study to divide the
questionnaire into mental and physical fatigue components for separate analysis. Compared to
the general population, adults with CP report significantly more physical, but not more mental
fatigue. Despite the overwhelming evidence that physical fatigue is a significant impairment in
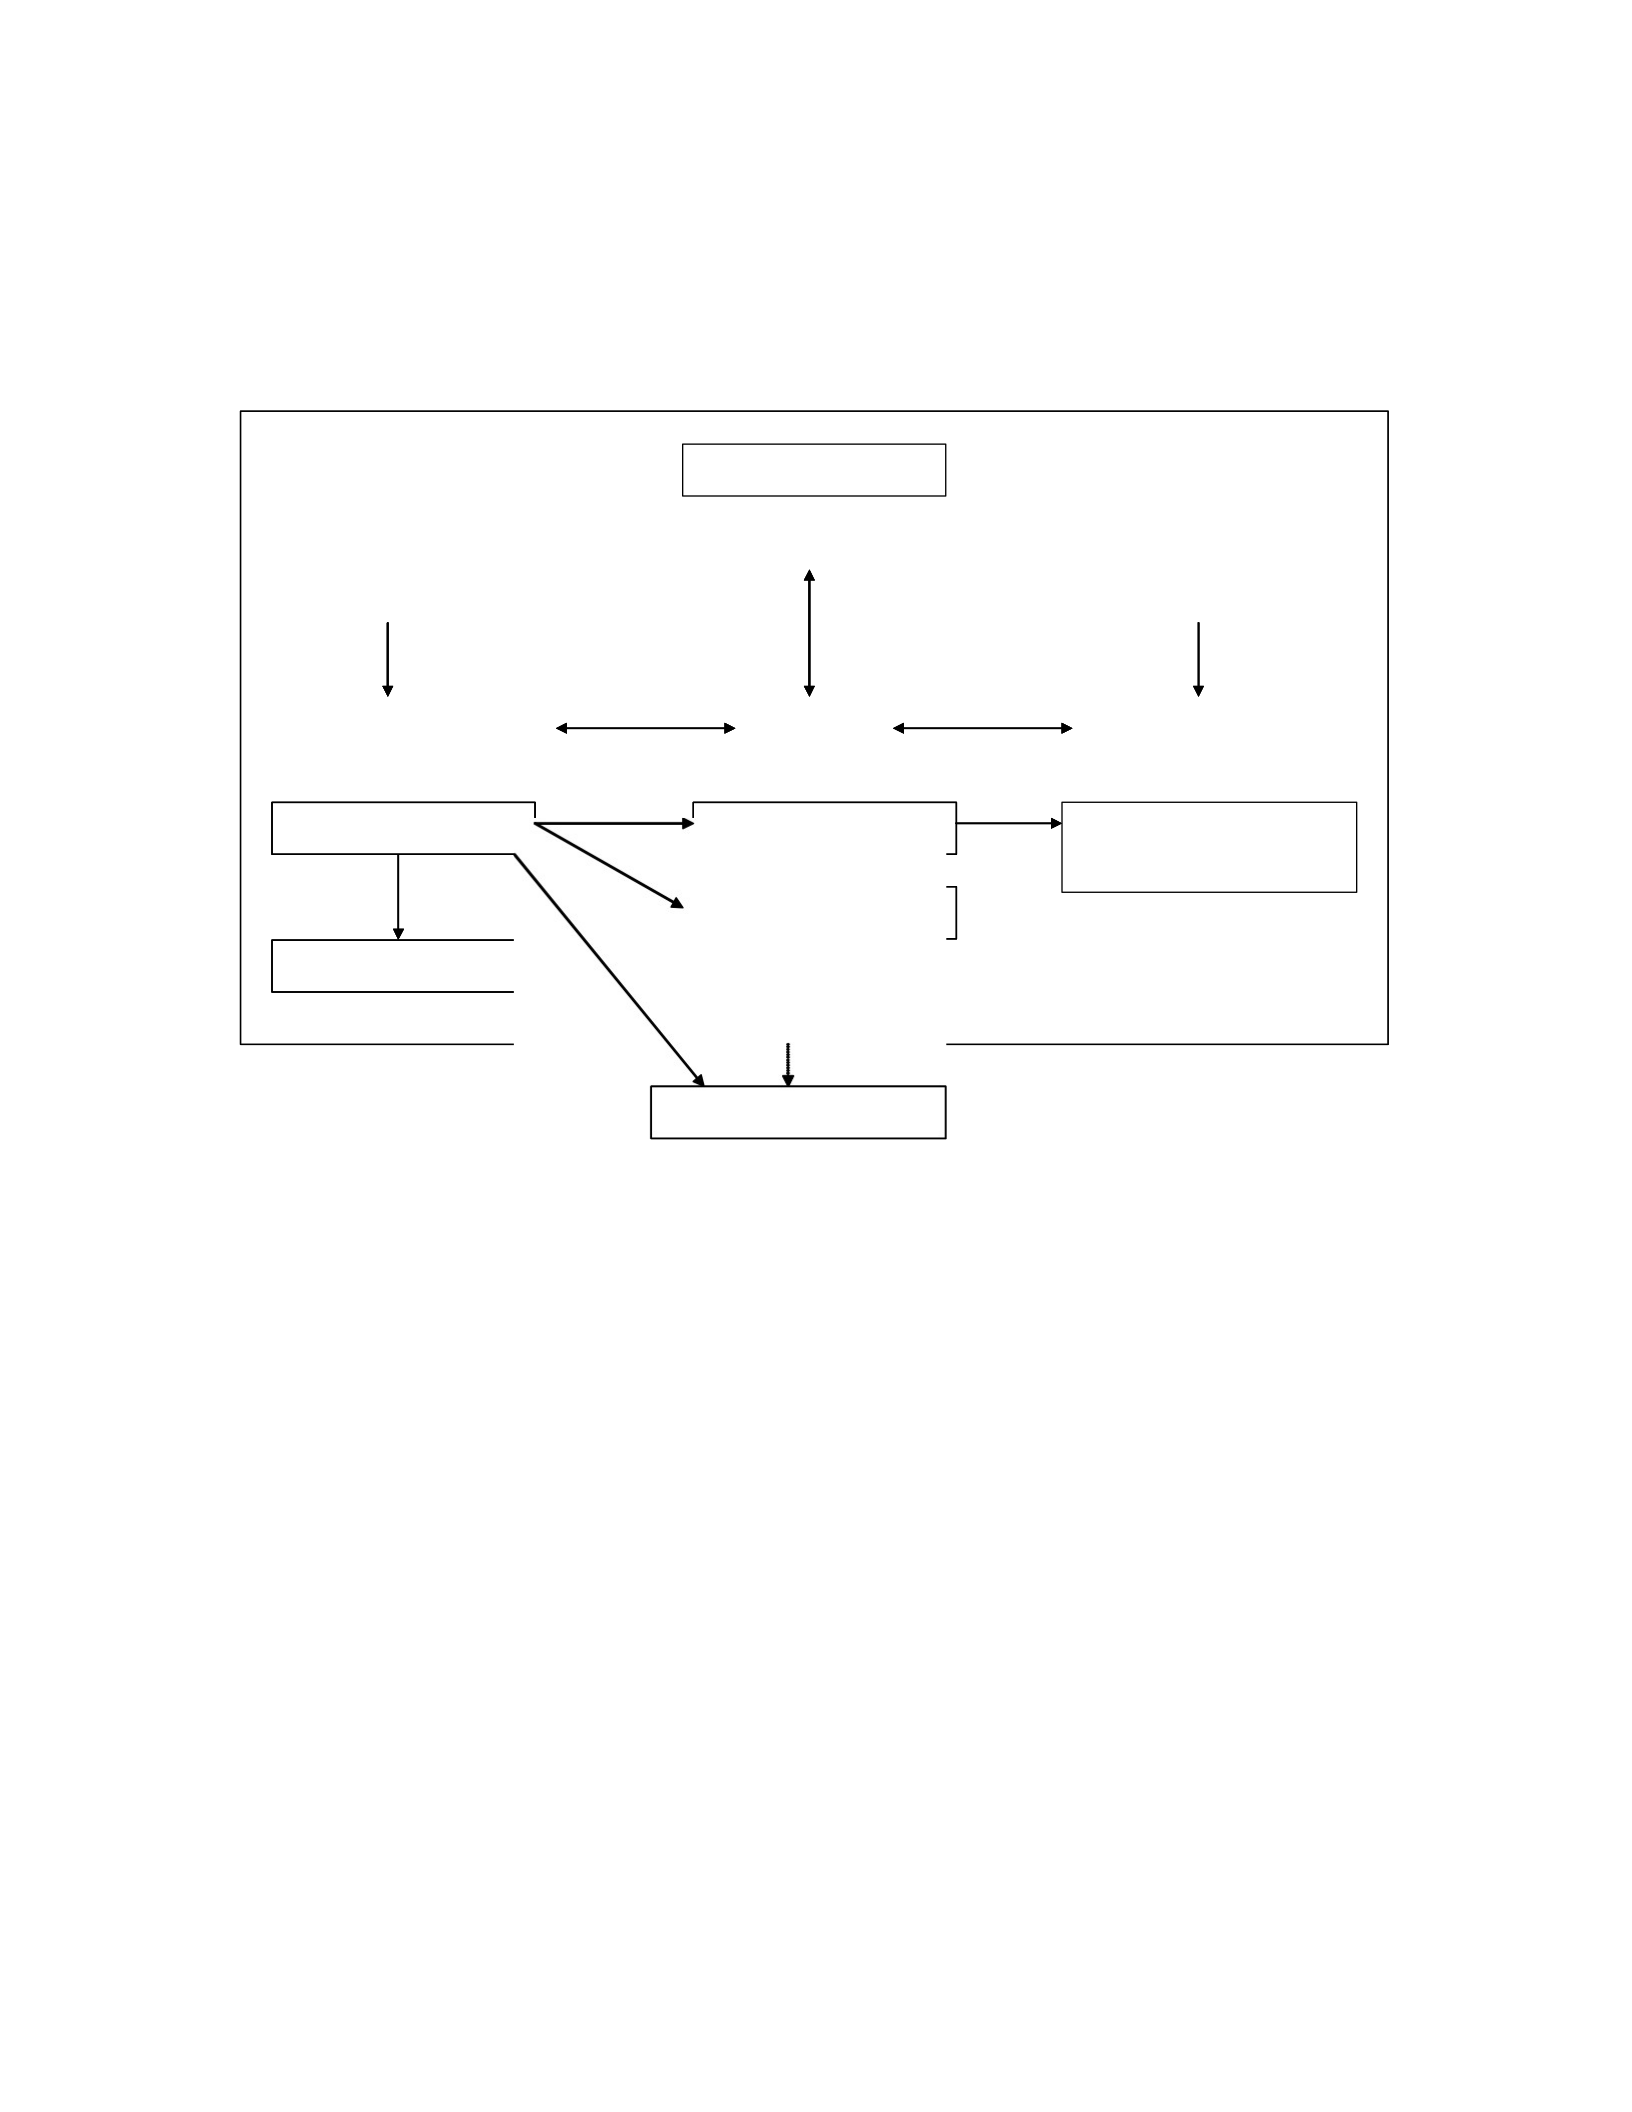
Pain
Functional
Skills
Ambulation
FATIGUE
ParticipationActivity
Body structures
and functions
Health condition
Life Satisfaction
Emotional/Physical
role function
Cerebral Palsy
89
this population, there are no studies to date that have quantitatively assessed physical fatigue in
this population.
“Quality of Life”
Figure A.2. The World Health Organization’s International Classification of Functioning,
Disability and Health (ICF, 2001) illustration of the relationships between fatigue (body
function) and activity limitations and participation. The relationship between fatigue and low
life satisfaction is also illustrated.
Further support for the existence of muscle fatigue in individuals with CP comes from
studies of energy expenditure. Because of the frequent clinical observation of fatigue in children
with CP, previous studies have investigated cardiovascular endurance (Lundberg, 1978; Rose,
Haskell, & Gamble, 1993; Unnithan, Dowling, Frost, & Bar-Or, 1996). Rose et al. (1993)
demonstrated that the cardiorespiratory response to walking at submaximal level of work was not
significantly different for children with cerebral palsy as compared to a healthy control group. In

90
addition, Dahlback and Norlin (1985) reported that children with CP became fatigued while
working at levels less than 50-60% of maximal oxygen uptake during treadmill walking,
indicating that local muscle fatigue was responsible for the exhaustion. Furthermore, McNevin,
Coraci, and Schafer (2000) observed a significant increase in perceived exertion without a
concomitant increase in heart rate during an incremental gait speed test. The authors suggest this
was possibly due to fatigue. Similar results have been observed in the upper extremities of
children with CP. In one study, cardiorespiratory endurance during an arm ergometer test did not
differ between subjects with CP and controls at 75% VO2 and maximum heart rate (Tobimatsu,
Nakamura, Kusano, & Iwasaki, 1998). Subjects with CP also stopped the ergometer test
prematurely at 75% VO2 max because of arm muscle fatigue. Collectively, this evidence
provides support that local muscle fatigue rather than cardiorespiratory factors may be
responsible for the exhaustion observed in submaximal states.
Fatigue has also been studied extensively in other neurological populations with upper
motor neuron lesions that present with spasticity and other similar impairments to those seen in
CP. Although there are similar documented complaints of fatigue in other neurological
populations via questionnaires and fatigue scales (Sharma, Kent-Braun, Mynhier, Weiner, &
Miller, 1995; Staub & Bogousslavsky, 2001), objective assessments of fatigue have been
measured. Muscle fatigue, in particular, has been quantitatively assessed in MS and spinal cord
injury (SCI) (de Haan A., de Ruiter, van der Woude, & Jongen, 2000; Lambert, Archer, &
Evans, 2001; Lenman, Tulley, Vrbova, Dimitrijevic, & Towle, 1989; Miller, Green, Moussavi,
Carson, & Weiner, 1990). Muscle fatigue as used here is defined as a decline in the force-
generating capacity of the neuromuscular system, which occurs during sustained activity
(Bigland-Ritchie, Johansson, Lippold, & Woods, 1983). The commonality among these studies is
that muscles of individuals with MS and SCI are more fatigable than those without pathology.

91
Perhaps the most extensive evidence of muscle fatigue in neurological populations is
from studies of MS, as fatigue is one of the most common and disabling symptoms in this
disease (Schwid et al., 2002). However, unlike CP, MS is a progressive neurological disorder
with differing pathology. The most similar upper motor lesion to CP would be cerebrovascular
accident (CVA), characterized by unilateral damage to the cerebral cortex. However, studies on
this population are limited, and results are equivocal. When comparing the involved to the
uninvolved contralateral side, decreased levels of fatigue (Riley & Bilodeau, 2002; Toffola,
Sparpaglione, Pistorio, & Buonocore, 2001) and no significant differences (Sunnerhagen,
Svantesson, Lonn, Krotkiewski, & Grimby, 1999; Svantesson, Osterberg, Grimby, &
Sunnerhagen, 1998; Svantesson, Sunnerhagen, Carlsson, & Grimby, 1999) were observed. The
discrepancy among studies may be explained by differing methodology, muscles studied, and
subject characteristics. Methodological differences include the use of electrical stimulation
techniques (Riley et al., 2002; Toffola et al., 2001), isokinetic dynamometry (Sunnerhagen et al.,
1999; Svantesson et al., 1999), and the standing heel-rise test (Svantesson et al., 1998), which
may partially explain the different results. In fact, the heel-rise has not been validated as a
measure of fatigability. Riley and Bilodeau (2002) studied the upper extremity, where the others
studied different lower extremity muscles. Among the studies where no differences were
observed, the subjects were ambulatory with only minor motor impairment. In fact, two of the
three studies reported that spasticity was absent (0 on the Ashworth Scale) in the studied
plantarflexors of all subjects (Svantesson et al., 1998; 1999). The mild impairment level of these
subjects may explain why there were no observed differences between the paretic, non-paretic,
and control sides. Regardless of the measurement technique utilized, considering that we know
the ipsilateral “uninvolved” extremity is often affected in CVA (Baskett, Marshall, Broad,
Owen, & Green, 1996), it may not be valid to compare the two sides without a control group. In

92
summary, CP is a lifelong disorder, which distinguishes it further from these other neurological
disorders and as such, these results cannot be extrapolated to CP without further investigation.
Purpose and Clinical Significance
The purpose of this paper is to review the evidence implicating muscle fatigue as a
significant impairment in people with CP and to discuss potential contributors of fatigue in this
population. Although previous research has focused on the amelioration of spasticity as a
primary goal of treatment, current research has shown that other aspects of muscle performance,
such as strength, have higher correlations with gross motor function and walking velocity, and
are amenable to treatment (Damiano & Abel, 1998; Damiano, Kelly, & Vaughn, 1995; MacPhail
& Kramer, 1995). A critical aspect of muscle performance is endurance, or resistance to fatigue,
and this area of performance has not been substantiated in individuals with CP. Therefore, a
better understanding of muscle fatigue or endurance in this population and its relationship to
other impairments and activity limitations will lead to improved treatment programs. Improved
treatment aimed at addressing fatigue may ultimately improve the health related quality of life in
these individuals, thereby delaying the onset of worsening disability with age.
Muscle Fatigue
Definition
Because of the broad use of the term fatigue, it is important to operationally define
fatigue. For purposes of this review, muscle fatigue will be defined as a reduction in the force-
generating capacity of the neuromuscular system, which occurs during sustained activity
(Bigland-Ritchie et al., 1983). Muscle endurance, on the other hand, is resistance to fatigue or the
ability to withstand fatigue. These terms are often used interchangeably throughout the literature
with muscle endurance tests often employed to assess muscle fatigue (Jones & Stratton, 2000).

93
Mechanisms
Fatigue is a common occurrence in the everyday life of individuals with neurological
disorders as well as in able-bodied individuals (Sharma et al., 1995; Staub & Bogousslavsky,
2001). The perception of fatigue is very subjective, with complaints such as feelings of
weakness, lack of energy, and lassitude. Objectively, however, fatigue has been defined as a
reduced capacity to maintain a required physical or mental output (Staub & Bogousslavsky,
2001). Although not the focus of this paper, it is important to mention that fatigue can occur in
several different central and peripheral sites, such as the following: 1.) primary motor cortex
activation, 2.) central nervous system drive to motor neurons, 3.) muscles and motor units that
are activated, 4.) neuromuscular propagation, 5.) excitation-contraction coupling, 6.) the
availability of metabolic substrates, 7.) intracellular mechanisms, 8.) contractile apparatus, and
9.) muscle blood flow (Bigland-Ritchie, 1981). Traditionally, fatigue was thought to occur
exclusively either in the central nervous system or the peripheral nervous system. However,
since muscle activity depends on the integrity of the entire chain of events, fatigue may occur at
many sites simultaneously (McComas, Miller, & Gandevia, 1995). Thus, fatigue should be
viewed as the result of the interaction of several different processes in both the central and
peripheral nervous system.
Contributors to Muscle Fatigue in Individuals with CP
Introduction
Central nervous system lesions may cause impaired central drive to the motoneurons, or
central fatigue. However, it is not specific to the underlying disorder. In other words, upper
motor neuron lesions do not exclusively induce central fatigue as a consequence of the lesion
site. Rather, individuals with upper motor neuron disorders generally demonstrate both central
and peripheral fatigue factors (de Haan A. et al., 2000; Lenman et al., 1989; Miller et al., 1990).
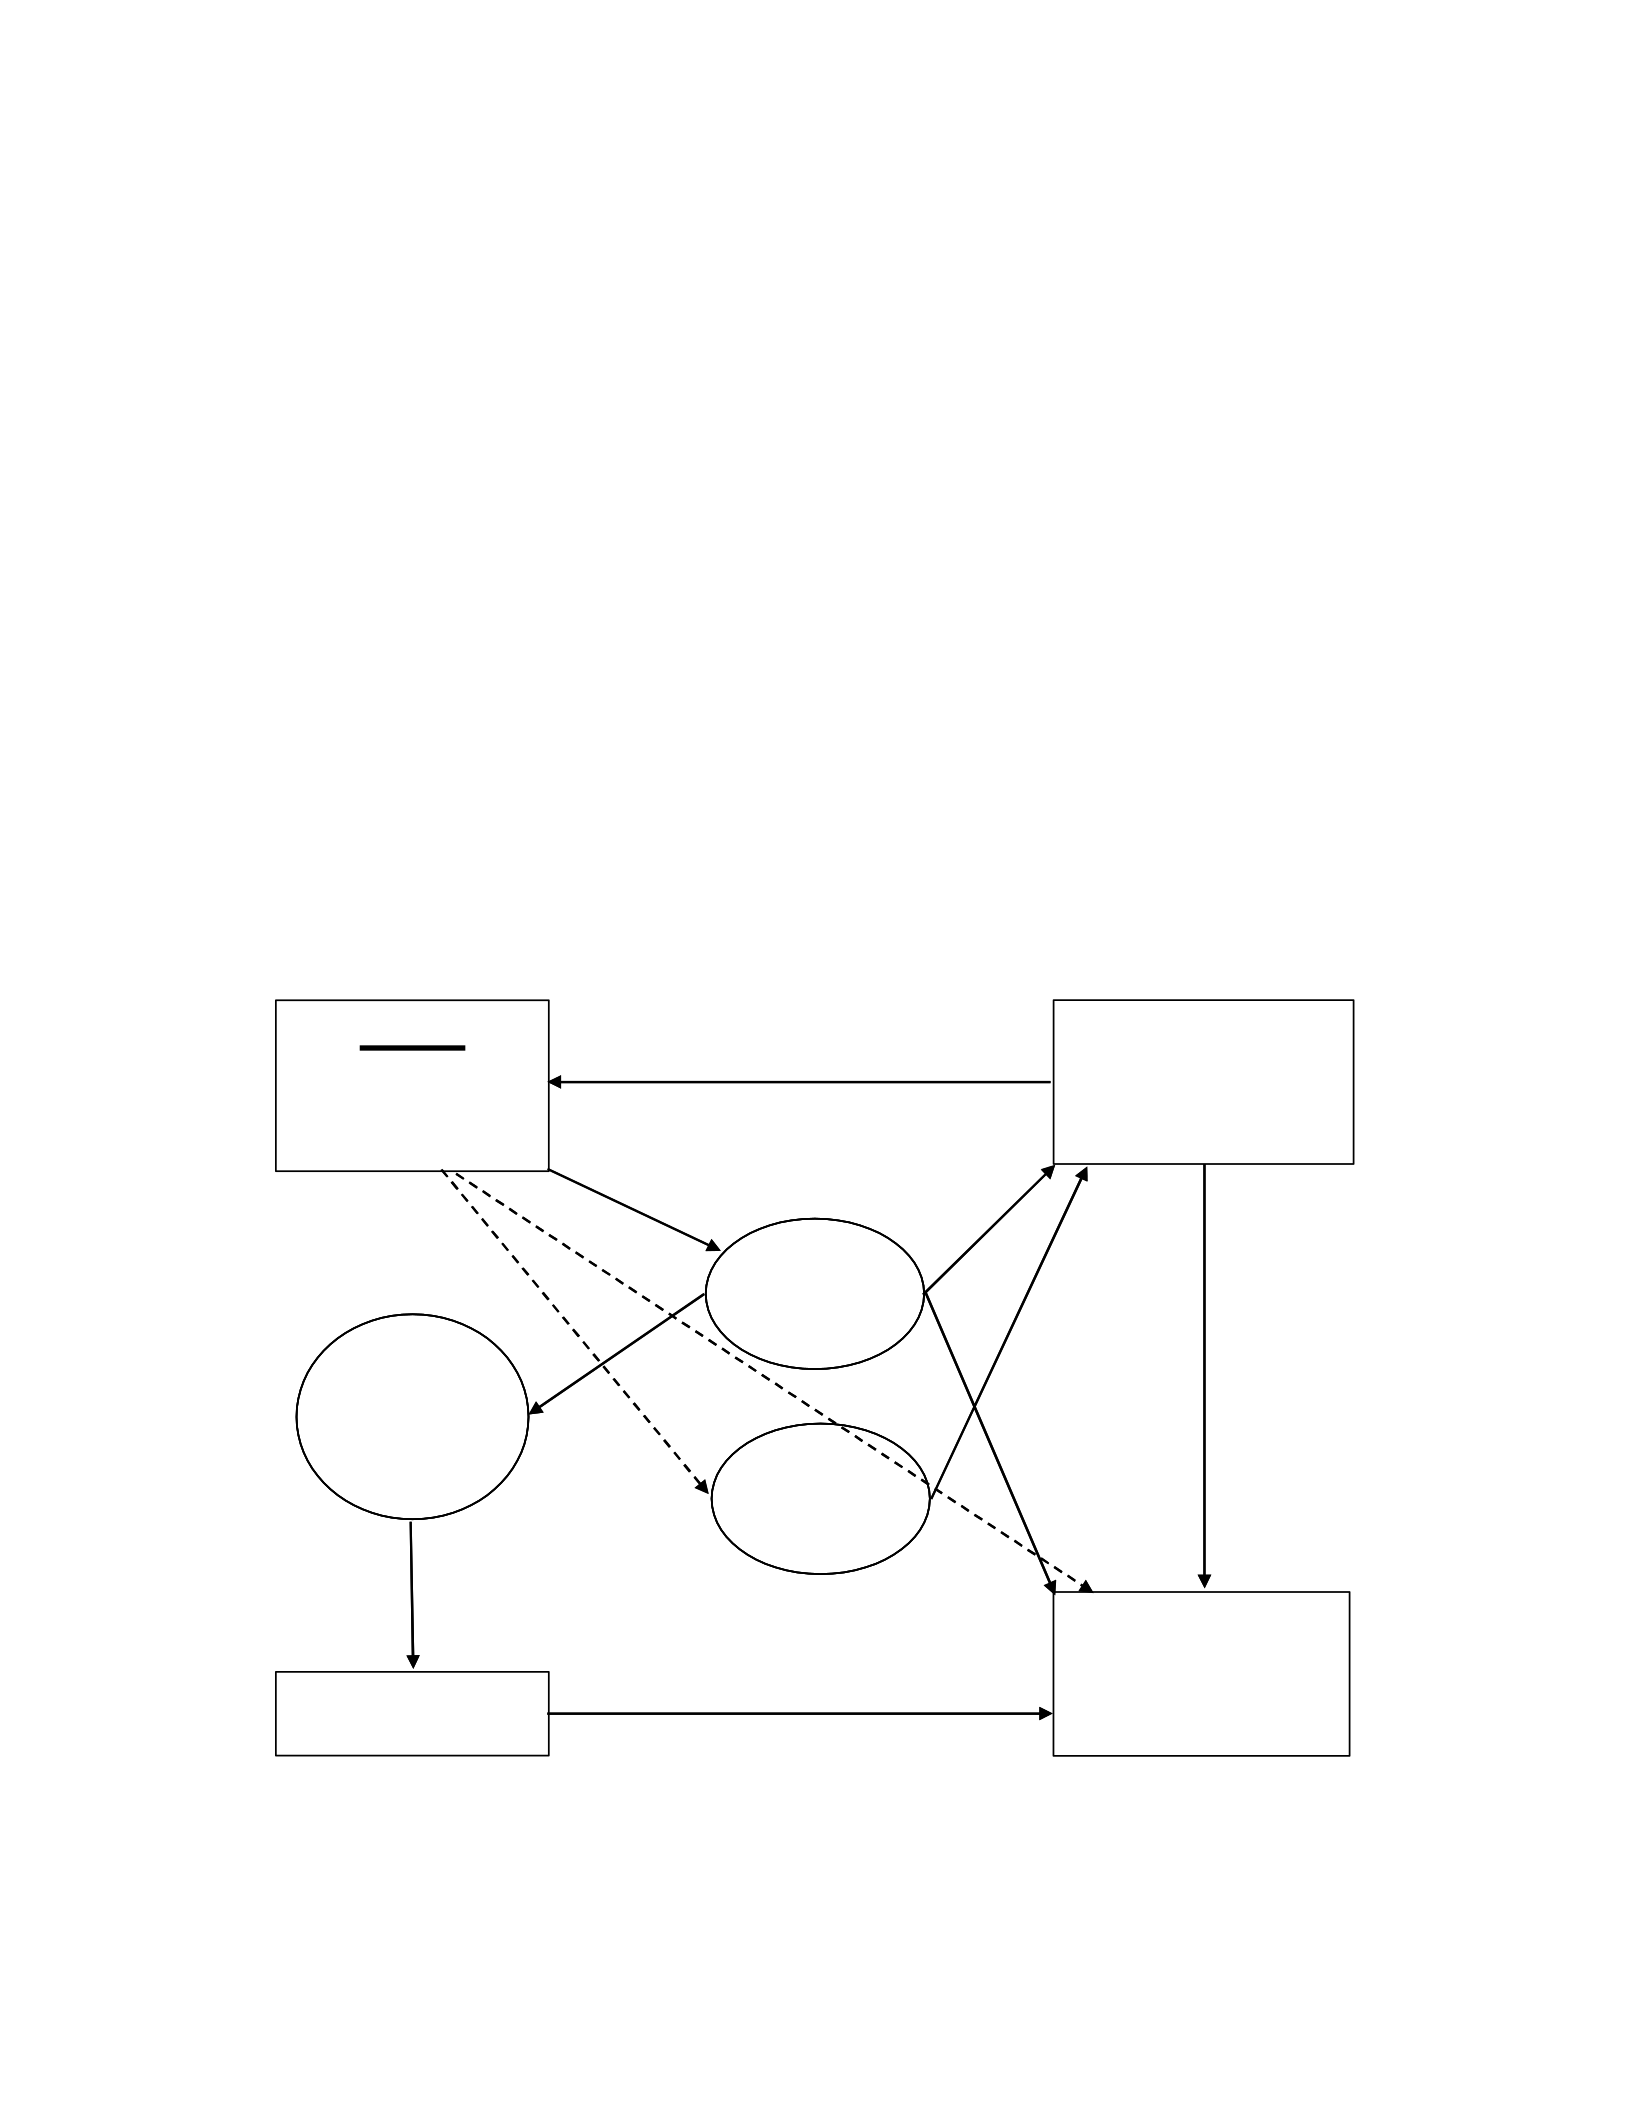
Disus
e
Muscle
Propertie
sIncrease
d
effort
UMN
Hypertonia
Weakness
Cocontraction
LMN
Muscle
Fatigue
↓ Central
Drive
94
The relationships among these factors are usually quite complex and vary among disorders
(Figure A.3).
In addition to these factors, CP is a multifaceted disorder and as such, complex
interrelationships exist among upper motor neuron lesion impairments. The relationships among
muscle fatigue and other impairments are important in the understanding of fatigue, as these
impairments may, in fact, contribute directly or indirectly to muscle fatigue. As a result, four
contributors to fatigue at the impairment/body function level have been identified and will be
discussed: weakness, co-contraction, spasticity, and stiffness. Muscle adaptations in spastic
disorders will be also be highlighted, as these factors may play an important role in the process
of fatigue (Figure A.3).
Figure A.3. Diagram illustrating the relationships between central and peripheral factors of
muscle fatigue in upper motoneuron (UMN) lesions. (LMN = lower motoneuron).
Modified from McComas et al., 1995.

95
Muscle Adaptation in Spastic Disorders
Definitions
Lesions to the central nervous system, also known as upper motor neuron lesions, result
in hypertonia or an increased resistance to passive muscle elongation (Stolov, 1966).
Unfortunately, the term “spasticity”, a component of hypertonia, is frequently and non-
specifically used to describe all aspects of hypertonia in addition to other upper motor neuron
signs, such as clonus and spasms. Hypertonia is associated with an increased sensitivity of the
stretch reflex (reflex component) and with changes in muscle and connective tissue properties
(non-reflexive component) (Malouin, Bonneau, Pichard, & Corriveau, 1997). The reflexive
component, also know as spasticity, is defined as a velocity-dependent increased resistance to
movement due to hyperexcitable stretch reflexes (Lance, 1980). Passive stiffness, on the other
hand, denotes the non-reflexive components, such as changes in muscle tissue, joint capsules,
and surrounding connective tissue, which are not velocity-dependent (Singer, Dunne, & Allison,
2001). Rather, stiffness is a length-dependent resistance to movement. It should be noted that
there is also a non-reflexive, velocity dependent component known as viscosity. However,
viscosity has been observed to contribute insignificantly to passive resistance in CP (Damiano,
Quinlivan, Owen, Shaffrey, & Abel, 2001). For clarity, the terms spasticity (reflexive) and
stiffness (non-reflexive) will be used throughout the review paper as described above.
Introduction
Although the primary lesion of CP is neural, it is important to discuss the properties of
spastic muscle. It has been well established that muscle properties adapt to the amount and type
of neural stimulation that is imposed upon them. Therefore, investigation of the muscle changes
which occur secondary to CP can provide insight into the effects of the disease process on
muscle characteristics over an extended period of time (Lieber, Steinman, Barash, & Chambers,

96
2004). In general, fiber type distribution and muscle fiber size are indicators of the amount and
type of activity imposed upon a muscle and as such, are often investigated in spastic muscle in
order to determine a muscle’s usage pattern (Lenman et al., 1989; Miller et al., 1990; Rose et al.,
1994). Predominance of a particular fiber type can influence fatigue, as Type I (slow twitch)
fibers are more fatigue-resistant, while Type II (fast twitch) fibers are more fatigable (Burke,
Levine, Tsairis, & Zajac, 1973; Thorstensson & Karlsson, 1976). Therefore, the investigation of
fiber type predominance in individuals with CP will provide insight into muscle fatigue in this
population.
Increased/Decreased Use Models
Two models of muscle usage have been extensively described in the literature and serve
as templates to describe the changes that occur in skeletal muscle with either increased or
decreased use. Increased use models, such as chronic electrical stimulation or endurance
exercise, result in muscle fiber hypertrophy and an increased percentage of type I, slow and
oxidative, fibers due to transformation of fast to slow twitch fibers (Eisenberg & Salmons, 1981;
Lieber, 1986; Roy, Meadows, Baldwin, & Edgerton, 1982). On the other hand, decreased use
models, such as reduced activity, immobilization, and spinal cord isolation or injury, result in
muscle fiber atrophy and transformation to a greater proportion of type II, fast and glycolytic,
fibers (Booth & Kelso, 1973; Grossman, Roy, Talmadge, Zhong, & Edgerton, 1998; Lieber,
Friden, Hargens, & Feringa, 1986a; Lieber, Johansson, Vahlsing, Hargens, & Feringa, 1986b).
Two schools of thought have emerged regarding the effect of spasticity on muscle properties.
One is that spasticity leads to muscle disuse, while the other purports that spasticity results in
chronic muscle overactivity as seen in increased use models (Lieber et al., 2004). Although it
appears likely that spasticity represents an increased use model due to chronic over-activity,
there has been no consensus on fiber type predominance in spastic disorders. There are biopsy
97
reports of increased percentages of Type I fibers (Dietz, Ketelsen, Berger, & Quintern, 1986; Ito
et al., 1996; Marbini et al., 2002; Rose et al., 1994), increased percentages of Type II fibers
(Carroll, Gallagher, Seidle, & Trappe, 2005; Kent-Braun et al., 1997; Ponten, Friden, Thornell,
& Lieber, 2005; Sjostrom, Fugl-Meyer, Nordin, & Wahlby, 1980), or no change in fiber type
distribution (Booth, Cortina-Borja, & Theologis, 2001; Castle, Reyman, & Schneider, 1979;
Romanini, Villani, Meloni, & Calvisi, 1989). As a result, it appears that spastic muscle may not
be adequately represented by either model. These conclusions in the literature regarding the
effect of spasticity on muscle properties are deduced across a wide range of diagnoses with
spasticity (Lieber et al., 2004). Therefore, it is important to discuss the muscle properties in
individuals with CP alone, as these other diagnoses (MS and SCI) may present confounding
issues, such as adult versus pediatric onset of spasticity.
Muscle Properties in Individuals with CP
Specific to individuals with CP, literature suggests that there may be significant
secondary effects of CP on muscle tissue itself. Muscle abnormalities such as changes in muscle
fiber size and fiber type distribution, collagen accumulation, and increased stiffness of spastic
muscle cells have been extensively reported (Booth et al., 2001; Castle et al., 1979; Friden &
Lieber, 2003; Ito et al., 1996; Marbini et al., 2002; Romanini et al., 1989; Rose et al., 1994). A
common finding among these studies, however, is an increase in fiber size variability, which is
representative of a pathological but non-specific skeletal muscle abnormality (Lieber et al.,
2004).
However, there is also no general consensus as to whether spastic muscles in individuals
with CP represent an increased or decreased use model. For example, Ito et al., Marbini et al.,
and Rose et al. identified a predominance of Type I fibers, while Castle et al. and Romanini et al.
showed no change. Methodological issues regarding biopsy studies include the number of fibers

98
sampled, the variability in fiber type and fiber size between muscles, whether different muscles
are being used to compare control subjects to those with pathology, and the variability in severity
of disease or clinical presentation (Lieber et al., 2004). These studies sampled muscle fibers
across numerous different muscles and in a wide range of ages (Castle et al., 1979; Ito et al.,
1996; Marbini et al., 2002; Romanini et al., 1989; Rose et al., 1994). In addition, only 200 to 300
fibers per biopsy were sampled (Castle et al., 1979; Ito et al., 1996; Marbini et al., 2002;
Romanini et al., 1989; Rose et al., 1994) or no specifics were reported (Marbini et al., 2002;
Romanini et al., 1989). Only one study had a control group but examined historical pathological
specimens from different muscles (Rose et al., 1994). Therefore, it is not surprising that there is
no general consensus as to whether muscles in individuals with CP represent an increased or
decreased use model.
An issue that has not been addressed in these biopsy studies of “spastic” muscle is the
degree of spasticity present, if any, in the muscles sampled. Both clinically and experimentally,
it is common to be unable to detect spasticity in certain muscle groups while detecting it in
others (Damiano et al., 2002; Damiano et al., 2001; Katz, Rovai, Brait, & Rymer, 1992).
Therefore, if spasticity is believed to result in secondary myopathic changes, the presence and
degree of spasticity should be documented for the muscles in question. Until this is documented
and investigated experimentally, we cannot accurately say that these findings are representative
of “spastic” muscle. Rather, these histopathological results are representative of muscles
involved in upper motor neuron lesions. With this in mind, Ponten et al. (2005) indirectly
provided insight into the preferential affect of spasticity on muscle properties in CP. The aim of
this study was to determine whether different muscle groups in the same individuals with CP are
affected differentially by the disease process. Therefore, biopsies of the wrist flexors and
extensors were sampled in the same individuals with CP. Furthermore, Ponten et al. addressed

99
some of the

100
earlier methodological concerns by testing a smaller age range of five years and sampling over a
thousand fibers per biopsy. Results revealed increased fiber type variation and decreased fiber
size for the wrist flexors as compared to the extensors. More importantly, there was a
significantly greater percentage of type IIb, fast fatigable, fibers in the flexors as compared with
the extensors. It is well known that spasticity affects the upper extremity flexors greater than the
extensors and for this reason, the wrist flexors are often the site of tendon transfers (Friden &
Lieber, 2003; Katz et al., 1992). Although spasticity was not measured in this study, all subjects
were undergoing tendon transfers or flexor tendon lengthenings. Therefore, we can infer with
some degree of confidence that the wrist flexors were spastic and had greater levels of spasticity
than the extensors. The authors concluded that the increased percentages of Type IIb fibers and
decreased fiber size in the wrist flexors as compared to the extensors provides the most sound
evidence that spasticity in CP may represent a decreased-use model. However, further research is
needed to verify this assumption.
Weakness
The presence of weakness in muscles of individuals with CP as compared to age-
matched controls has been well documented (Damiano, Vaughan, & Abel, 1995; Wiley &
Damiano, 1998). The exact nature of the weakness is unclear and is thought to be a result of
either decreased central drive to the agonist due to the lesion itself, spasticity, co-contraction,
secondary changes in the properties of the muscles fibers, or some combination of the above
(Damiano et al., 2001). In fact, leg strength has been observed to be correlated to self-selected
walking speed and to the Gross Motor Function Measure (GMFM) in children and adolescents
with CP (Damiano & Abel, 1998; Kramer & MacPhail, 1994). As a consequence, weakness is
considered one of the primary contributors to motor dysfunction in individuals with CP.

101
Weakness in upper motor neuron disorders is often accompanied by disuse, as the
individual tries to conserve strength by resting or by ceasing to perform tasks that are tiring.
Disuse can reduce the ability of the higher motor centers to recruit motoneurons maximally,
leading to fatigue (McComas et al., 1995). As discussed previously, muscles respond to the
amount and type of activity that is imposed upon them. Disuse, or decreased use models, result
in muscle fiber atrophy and transformation to a greater proportion of type II, fast and glycolytic,
fibers (Booth & Kelso, 1973; Grossman et al., 1998; Lieber et al., 1986a; Lieber et al., 1986b).
Therefore, weakness can also lead to increased numbers of type II fibers, which are more
fatigable. As a result, weaker muscles may demonstrate greater levels of fatigability.
A secondary consequence of weakness and muscle atrophy is the recruitment of more
motor units or the greater frequency of excitation required to perform a given task (Edgerton,
Roy, Allen, & Monti, 2002). Normally, the force of a muscular contraction is determined by both
firing rate or rate modulation and the recruitment of additional motor units (Deluca & Erim,
1994). In addition, smaller motor units are recruited first, followed by larger motor units. This
regulation serves to decrease the occurrence of fatigue by ensuring that the larger, more fatigable
units are recruited later in the contraction (Calcancie & Bawa, 1990). Recruitment and rate
modulation have been shown to be impaired in stroke patients with hemiparesis (Gemperline,
Allen, Walk, & Rymer, 1995; Jakobsson, Grimby, & Edstrom, 1992; Rosenfalck & Andreassen,
1980). In particular, Gemperline et al. studied the upper extremity muscles of six subjects with
hemiparesis and showed that motor units were recruited at lower thresholds and failed to
increase firing rates with increased muscle activation. As a result, additional force was generated
primarily through increased recruitment rather than rate modulation. They concluded that the
inability to increase firing rates may alter the precise match between the properties of the
motoneuron and the mechanical properties of the muscle fibers, leading to fatigue and weakness.

102
As a consequence of recruiting more motor units, the overall fatigability will increase because
increased numbers of upper threshold units will be recruited.
Working at a higher capacity during everyday tasks secondary to weakness was first
described by Pimm (1992) as “physiological burn-out” in adults with CP. In other words,
working at a greater load relative to maximum on a daily basis can cause the system to become
overburdened and physical function to deteriorate (de Haan A. et al., 2000; Pimm, 1992).
Deterioration of function leads to disuse. Disuse exacerbates weakness, and a vicious cycle
develops. Combined with an increase in perceived effort, fatigue is sure to develop.
Co-contraction
Co-contraction refers to the simultaneous activation of agonist and antagonist muscles
during voluntary movement. Although co-contraction occurs normally in everyday activities, it is
excessive in individuals with CP. Co-contraction in persons with upper motor neuron lesions is
thought to be caused by reciprocal facilitation/excitation of the agonist and antagonist
(Myklebust, Gottlieb, Penn, & Agarwal, 1982) or decreased disynaptic or presynaptic reciprocal
inhibition of the antagonist muscle during agonist activation (Morita, Crone, Christenhuis,
Petersen, & Nielsen, 2001). Co-contraction has been suggested to generate opposing torque
throughout the range of motion (Baratta et al., 1988). In addition, it may impair the full
activation of the agonist due to reciprocal inhibition (Milner, Cloutier, Leger, & Franklin, 1995;
Tyler & Hutton, 1986). Therefore, co-contraction could reduce the efficiency of force output,
leading to fatigue. It is of importance to note that neither the antagonistic moment (Kellis, 2003)
nor the electromyography (EMG) activity (Kellis & Kellis, 2001) has been shown to change
during an isokinetic fatigue task in pubescent boys. Therefore, the contribution of the antagonist
co-contraction to the force output should remain constant throughout a fatigue task.

103
Further support for this hypothesis comes from studies of energy expenditure during
gait in children with CP. It has been established that children with CP have a lower maximal
oxygen uptake (VO2 max) as compared with able bodied peers during tests of cycling and
treadmill walking (Hoofwijk, Unnithan, & Bar-Or, 1995; Lundberg, 1978). On average they
also have a three-fold increase in submaximal walking energy expenditure (Campbell & Ball,
1978).
Dahlback and Norlin (1985) reported that children with CP became fatigued while working at
submaximal levels less than 50-60% of maximal oxygen uptake during treadmill walking. They
concluded that local muscle factors rather than cardiopulmonary factors were responsible for the
exhaustion. Furthermore, Unnithan et al. (1996) reported a positive relationship between co-
contraction of lower extremity muscles in children with CP and the elevated energy cost of
treadmill walking at submaximal speeds. Children with CP also complain of fatigue at these
submaximal walking intensities considered slow for able-bodied peers (Berg, 1970; Dahlback &
Norlin, 1985; Unnithan et al., 1996). Therefore, high levels of co-contraction may be responsible
for the early fatigue of muscles, thereby contributing to the reduction in VO2 max at maximal
exercise intensity.
Spasticity
It is well-recognized that many children with CP have spasticity, or a velocity-dependent
increased resistance to movement due to hyperexcitable stretch reflexes (Lance, 1980).
Although spasticity was once considered the primary cause of motor dysfunction in individuals
with CP, it is now believed that other impairments, such as weakness, are more detrimental to
function (Damiano & Abel, 1998; Sahrmann & Norton, 1977). Furthermore, spasticity has been
observed to have a weak to absent relationship to strength (Damiano et al., 2001; Ross &
Engsberg, 2002) and only a weak to moderate relationship to function (Damiano et al., 2001).

104
Since muscle endurance, like strength, is also a component of muscle performance, perhaps
spasticity will

105
have a weaker or no relationship to muscle endurance as well. Nevertheless, spasticity is an
important component of the upper motor neuron syndrome. Therefore, the potential long-term
and short-term effects of spasticity on muscle fatigability are worth investigating.
In regards to long-term muscle adaptation to spasticity in CP, there is no consensus on
whether spasticity represents an increased or decreased use model (Booth et al., 2001; Castle et
al., 1979; Ito et al., 1996; Marbini et al., 2002; Ponten et al., 2005; Romanini et al., 1989; Rose
et al., 1994). If spasticity leads to disuse, then spastic muscles should be more fatigable due to
increased numbers of Type II fibers as seen in decreased use models. In turn, if spasticity leads
to muscle overactivity, then spastic muscles should be more fatigue-resistant due to increased
numbers of Type I fibers as observed in increased use models. Perhaps, fiber type predominance
may be dependent upon the muscle studied and the amount of spasticity in that particular
muscle. It is well established that different muscles have different fiber type distributions
(Edstrom & Nystrom, 1969); however, the relationship of fiber type to the amount of spasticity
has not been explored. The first histopathological study in CP reported a variety of patterns of
Type I/II atrophy and hypertrophy depending on the muscle biopsied and the degree of spasticity
or severity of each subject (Castle et al., 1979). However, a definitive relationship could not be
ascertained. Further support for this hypothesis stems from the original work of Ponten et al.
(2005). In this study, the presumed spastic wrist flexors were found to have increased amounts
of type II, fast fatigable fibers as compared to the less spastic wrist extensors. If the degree of
spasticity does indeed play a part in fiber type predominance, then the amount of spasticity
should influence the development of fatigue accordingly. Future muscle-specific biopsy studies
in conjunction with spasticity assessment are needed to explore this hypothesis.
It is important to note that these muscle fiber changes are the result of long-term
spasticity. However, fatigue is not solely determined by muscle fiber type. From a short-term

106
perspective, spasticity could impair the maximum force output of the agonist, secondary to the
hyperexcitable stretch reflex. Therefore, independent of fiber type changes, spasticity could also
result in an immediate reduction in the efficiency of force output, which would lead to fatigue.
Stiffness
Literature suggests that the properties of muscles in individuals with CP are very
different from normally developed muscles, including collagen accumulation (Booth et al.,
2001) and increased stiffness at both the cellular (Friden & Lieber, 2003) and whole muscle
level (Hufschmidt & Mauritz, 1985). This is of no surprise, considering the subjective
complaints of tightness and stiffness by individuals with CP and the resistance felt upon passive
movement of the extremities.
Dietz, Quintern, and Berger (1981) first suggested that that muscle hypertonia is mainly
due to secondary changes in spastic muscles and that these altered mechanical properties
contribute to muscle stiffness during gait. They observed increased EMG activity of the anterior
tibialis without a concomitant increase in ankle dorsiflexion during the swing phase compared to
controls. Furthermore, there was no excessive EMG activity of the gastroc/soleus and no
evidence of contracture. They concluded that the altered mechanical properties of the
gastroc/soleus muscle fibers themselves were responsible for the limited ankle dorsiflexion. This
hallmark study spurred numerous investigations into this phenomenon.
It has also been suggested that increased stiffness may be a compensation for weakness,
thus allowing better utilization of elastic energy during functional activities, such as gait
(Lamontagne, Malouin, & Richards, 2000; Svantesson & Sunnerhagen, 1997). Lamontagne et
al. reported that the passive stiffness contribution to the total plantarflexor moment in
individuals with CVA was greater on the weaker, affected side as compared to controls during
gait. Thus, the affected plantarflexors in subjects with CVA appeared to utilize passive stiffness

107
to

108
compensate for weakness as compared to the healthy controls. Svantesson & Sunnerhagen
(1997) reported a similar observation during controlled stretch-shortening cycles of the
plantarflexors in individuals with CVA. Furthermore, in a follow-up study in healthy adults,
fatigue, measured as the number of heel-rises performed to exhaustion, was negatively
correlated to the amount of stiffness (Svantesson, Carlsson, Takahashi, Thomee, & Grimby,
1998).
Increased stiffness was thus suggested to enhance the development of fatigue. Therefore,
stiffness, as a compensation for weakness, may be directly related to muscle fatigue.
Furthermore, stiffness (quantified as the slope of the torque/angle curve) has been observed to
have a stronger relationship to both strength and function as compared to quantitative measures
of spasticity (Damiano et al., 2002; Damiano et al., 2001). In accordance, perhaps stiffness will
have a stronger relationship to muscle fatigue than spasticity.
Methods of Measurement
Introduction
Muscle fatigue, or muscle endurance, has been studied using a wide variety of exercise
protocols and assessment methods. Based on the definition of muscle fatigue as a reduction in
the force-generating capacity of the neuromuscular system during sustained activity, the
different methods to measure muscle fatigue are discussed. The focus of this review is on
voluntary assessment techniques of muscular fatigue rather than electrical stimulation
procedures, such as tetanic stimulation and twitch interpolation. These electrical stimulation
techniques are used to differentiate between central and peripheral fatigue factors. The reliable
assessment of muscle fatigue is highly dependent upon the measurement of maximum force
generation and as such, maximal voluntary contraction force is considered the “gold standard”
for the assessment of fatigue (Vollestad, 1997). The advantage of using maximal voluntary force

109
is that the output is the result of the total chain of events, including both central and peripheral
fatigue factors.

110
Therefore, voluntary contraction should serve as the first choice of methods before additional
methods are employed to examine the possible sites within the central and peripheral systems
(Vollestad, 1997).
Fatigue Assessment in Children
Isometric and isokinetic techniques are most commonly employed in the assessment of
muscle performance in children. However, the limitations of isometric techniques are that the
strength measurements are limited to a fixed joint angle and optimal angles for individual muscle
groups in children have not been identified (Gaul, 1996). Despite the expense and complexity of
testing, isokinetic dynamometry is currently considered the most valid tool for muscle
performance assessment (Jones & Stratton, 2000). It provides a controlled, safe environment
where no resistance is applied once the movement has ceased. Although isokinetic testing in
children has typically been performed in the range of 0-240 degrees/second, an optimal
movement velocity for reliable measurement has not been established (Gaul, 1996; Jones &
Stratton, 2000).
Limited information regarding isokinetic muscle endurance testing in children is
available in the literature. To the author’s knowledge, there is only one study that has utilized
isokinetic dynamometry to assess the reliability of muscle fatigue testing in the knee flexors and
extensors of children. De Ste Croix, Armstrong, and Welsman (2003) studied 30, 12-year old
children on two test sessions separated by 1 week. The subjects performed 50 concentric,
reciprocal knee flexions and extensions at 90 degrees/second. A fatigue index was calculated by
using the average torque and average work of the first 3 and last 3 repetitions. The percentage
difference between these values was used to represent the decline in torque and work. Intra-class
correlation coefficients (ICCs) for knee extension torque fatigue and work fatigue were higher
(.90 and .85, respectively) than for flexion torque and work fatigue (.36 and .54, respectively). In

111
addition, all fatigue indices except for knee flexion torque fatigue index (.36), were deemed
reliable by high ICC values. After a sufficient recovery period, a second test of endurance was
performed consisting of reciprocal knee flexion and extension until the torque fell below 50% of
the maximal torque or the subjects reached 80 repetitions. Interestingly, none of the subject’s
extension or flexion torque fell below 50% of maximum after 80 repetitions. This testing
protocol has been frequently used in adults. Therefore, it is unclear as to why the subjects’
torque did not fall below the 50% of maximum in the allotted number of repetitions. The authors
suggested that it may be a function of the lower initial maximal torque values as compared to
adults. This idea is in agreement with Pincivero, Gear, Sterner, and Karunakara (2000) who
demonstrated that a faster rate of fatigue was significantly related to the ability to generate a high
initial level of torque. Kellis and Kellis (2001) utilized a similar protocol with reciprocal knee
flexion and extension at 60 degrees/second for approximately 60 seconds or 22 repetitions.
However, intersession reliability was not assessed for this protocol.
Fatigue Assessment in Cerebral Palsy
The first reported test of endurance in children with neuromuscular diseases was
published by Hosking, Bhat, Dubowitz, and Edwards (1976). For this test, the length of time the
leg could be held straight with the hip flexed to 45 degrees and the head at 45 degrees above the
horizontal were recorded with the subject in the supine position. Although this test was able to
discriminate between children with and without neuromuscular disease, it did not show sufficient
reproducibility to be recommended for future testing.
Other attempts to measure overall endurance in children with CP employed physiological
measures of energy expenditure, such as oxygen consumption, heart rate, perceived exertion, and
measures of cardiorespiratory function (Dahlback & Norlin, 1985; Hoofwijk et al., 1995;
Lundberg, 1976; Rose, Gamble, Burgos, Medeiros, & Haskell, 1990; Rose et al., 1993; Unnithan

112
et al., 1996). Others have studied endurance from an aerobic (Lundberg, 1978; Tobimatsu et al.,
1998) versus anaerobic perspective (Parker, Carriere, Hebestreit, & Bar-Or, 1992; Tirosh, Bar-
Or, & Rosenbaum, 1990). However, these are physiological measures of the overall individual
and are different from tests of muscle endurance. Proponents of anaerobic testing via the
Wingate anaerobic test purport to measure muscle endurance by measuring mean power of the
lower extremities (Parker et al., 1992). However, this test cannot differentiate between right and
left limb measurements or among muscle groups; therefore, it is a non-specific, gross
physiologic measurement of endurance. Isokinetic dynamometry, on the other hand, has the
ability to isolate a single muscle group under controlled conditions with stabilization of other
joints, thus providing a measure of localized muscle fatigue.
To date, there are no studies that have quantitatively assessed localized muscle fatigue
via isokinetic or isometric means in individuals with CP. However, because the basis of fatigue
or endurance testing is maximal voluntary contraction (Vollestad, 1997), it is important to
discuss the reliability of isokinetic strength testing in children with and without CP.
Isokinetic Strength Testing in Children With and Without CP
Two studies have examined the reliability of isokinetic strength assessments in children
and adolescents with CP (Ayalon, Ben-Sira, Hutzler, & Gilad, 2000; Van den Berg-Emons RJ,
Van Baak, de, Speth, & Saris, 1996). Both examined isokinetic concentric knee extension and
flexion but at different velocities of movement. Van den Berg-Emons et al. (1996) examined the
reliability of strength assessments in 12 children with CP (ages 6-12) on two separate tests
during the same day. Peak torque of the knee flexors and extensors was assessed over 5
maximum trials at 30, 60, and 120 degrees/second. Results revealed that the only reliable
measurement of peak torque for both the knee flexors and extensors was at 30 degrees/second
(Spearman rank correlation = rs= .71 - .84). However, it should be noted that knee flexion peak

113
torque was reliable at 60 and 120 degrees/second as well (rs =.75 and .65, respectively). These
results are questionable, considering that the two test sessions were performed on the same test
day with only an hour and a half break between tests. In addition, only two familiarization trials
were given. Therefore, the reliability at 60 and 120 degrees/second may have been significant
with a greater number of familiarization trials and increased time between tests.
A more recent study by Ayalon et al. (2000) investigated the reliability of strength
measurements in 12 children with CP (ages 9-15) on two separate occasions one week apart.
However, Ayalon et al provided 15 to 20 submaximal familiarization trials and utilized only one
velocity (90 degrees/second), which was determined to be the most comfortable for the
participants during a pilot study. Mean absolute peak torque and mean relative peak torque
normalized by body weight were the dependent measures. Results revealed both absolute and
relative peak torque measurements to be equally reliable with intrasession ICCs of .90 to .99 and
intersession ICCs of .95 to .99. In contrast with the Van den Berg-Emons et al study, knee
extension and knee flexion tests were both reliable at the faster speed of 90 degrees/second (ICC
intersession = .95-.98 and .96-.98, respectively). These results support the use of isokinetic
concentric testing at 90 degrees/second in children and adolescents.
Holland, McCubbin, Nelson, and Steadward (1994) were the first to investigate the
reliability of isokinetic concentric and eccentric strength testing in adults (ages 17-38) with CP.
Reliability of knee flexion and extension at 60 degrees/second was assessed over 3 test sessions
conducted every other day. All average torque and peak torque values were reliable except for
eccentric knee extension average torque, as determined by generalizability coefficients (p2 =.20).
In general, concentric tests were more reliable than eccentric tests (.69-.91 and .20-.90,
respectively). Furthermore, the concentric knee flexion test was more reliable than the knee
extension test (.80-.90 and .69-.91, respectively). Further support for the use of isokinetic

114
velocities greater than 30 degrees/second comes from strength testing in individuals with CVA,
during which reliability was established in normalized and non-normalized peak torque measures
at 90 and 60 degrees, respectively (Hsu, Tang, & Jan, 2002; Pohl, Startzell, Duncan, & Wallace,
2000). Collectively, these studies provide support for the use of higher speeds (60 – 90
degree/second), which have been speculated to mimic more functional speeds encountered in
everyday activities (Ayalon et al., 2000).
Studies of reliable strength assessment are more prevalent in healthy children than in
children with either neuromuscular or neurological disorders. Nevertheless, an optimal
movement velocity for isokinetic strength testing in children has not been established (Gaul,
1996; Jones & Stratton, 2000). However, reliability of strength measurements has been
demonstrated at 30, 60, 90, 100, 120, and 180 degrees/second for the knee flexors and extensors
in children and adolescents (De Ste Croix, Armstrong, & Welsman, 2003; Deighan, De Ste
Croix, & Armstrong, 2003; Kellis, Kellis, Gerodimos, & Manou, 1999; Merlini, Dell'Accio, &
Granata, 1995). In general, reliability for able-bodied children is higher for the knee extensors
compared to the knee flexors and for concentric versus eccentric testing.
Isokinetic Muscle Fatigue / Endurance Protocols
Adults
No single, reliable test of muscle endurance exists in children with or without CP.
Therefore, it is important to discuss endurance protocols in adults. The most widely used
protocol consists of a predetermined number of maximal repetitions. The number of maximal
repetitions in adults usually varies from 25 to 50 repetitions and is usually performed at 180
degrees/second (Burdett & Van Swearingen, 1987; Gleeson & Mercer, 1992; Manou, Arseniou,
Gerodimos, & Kellis, 2002; Pincivero, Gear, & Sterner, 2001; Pincivero, Lephart, &
Karunakara, 1997; Thorstensson & Karlsson, 1976). Another common protocol involves the

115
performance of

116
consecutive repetitions or maximum isometric contractions until the torque, work, or power
decreases to 50% of the maximum torque (Emery, Sitler, & Ryan, 1994; Schwendner, Mikesky,
Wigglesworth, & Burr, 1995). Other protocols require the subject to perform as many repetitions
as possible in a predetermined period of time (Felicetti, Zelaschi, & Di Patrizi, 1994;
Montgomery, Douglass, & Deuster, 1989) or repeated contractions until exhaustion (Patton,
Hinson, Arnold, Jr., & Lessard, 1978).
The most commonly used measurement parameter is the calculation of the fatigue index
(FI) as an indicator of muscle endurance. This idea was first proposed by Thorstensson and
Karlsson (1976), where the decline in torque output of the quadriceps after 50 contractions was
expressed as a percentage of the highest of the first 3 peak torques to the last 3 peak torques.
Although there is no standardized definition for FI, it usually represents the percentage decline
in work or torque from the beginning to the end of a predetermined number of repetitions or a
certain period of time. Thorstensson and Karlsson also reported a positive correlation between
the percentage of Type II fibers and the FI.
Although the most common technique, the FI has been questioned in terms of its
reliability (Burdett & Van Swearingen, 1987; Pincivero et al., 2001; Pincivero et al., 1997). With
similar protocols of 25 to 30 repetitions at 180 degrees/second, ICC’s have been reported from
.26 to .82 for knee extension and .52 to .84 for knee flexion. The disadvantages of the FI are that
it represents only the initial and final values. Furthermore, the division of one value with error
associated with it by another value with error associated with it results in a ratio with even more
error (Burdett & Van Swearingen, 1987). Because reductions in torque output over short periods
of time (30-60 seconds) have been observed to be linear (Bigland-Ritchie et al., 1983;
Lindstrom, Karlsson, & Gerdle, 1995), researchers have suggested the linear slope as an
alternative measure of the rate of decrease in work or torque over the testing session (Pincivero,

117
Gandaio, & Ito, 2003; Pincivero et al., 2001). The slope was found to be more reliable than the
FI with ICC’s of .78 to .82 (Pincivero et al., 2001). An advantage of using the slope is that it
captures the rate of decline over the entire test. However, the data must be linear in order to use
this measure of fatigue.
Emery, Sitler, and Ryan (1994) developed another alternative to the FI, in which fatigue
was measured by counting the number of repetitions completed in which three consecutive
repetitions met the 50% of peak torque deficit. They discovered that the number of repetitions
needed at 60 and 150 degrees/second, respectively, was 30 and 46 for knee extension and 36 and
41 for knee flexion. Burdett and Van Swearingen (1987) also calculated the number of
contractions until torque fell below 50% of maximum as well as a type of FI in which the ratio of
work done during the last 5 repetitions to the first five was measured. They determined that the
number of repetitions was more reliable (r = .85) than the FI/work ratio (r = .48). Similarly,
Manou et al. (2002) determined that the number of repetitions was very reliable for the knee
extensors and flexors (r = .82 and .90, respectively). Another measure of fatigability is endurance
time, or the time to reach either 50% of maximum or exhaustion (Manou et al., 2002; Patton et
al., 1978). The advantage of these two parameters is that they are simple and easy to calculate.
On the other hand, they do not provide a measure of the rate of decline. Furthermore, it has been
documented that endurance time is not closely related to fatigue (Vollestad, 1997).
Total work, or area under the isokinetic torque curve for all repetitions, is another
common measurement in endurance testing that has been determined to be highly reliable
(Burdett & Van Swearingen, 1987; Gleeson & Mercer, 1992; Manou et al., 2002). Again, with
similar protocols for the knee extensors and knee flexors, ICC’s were between .92 and .98 and
between .88 and .97, respectively. In fact, Gleeson and Mercer (1992) have proposed that total
work should be the recommended index of isokinetic leg muscular endurance. It has also been

118
suggested that the reliability of total work over all repetitions is a better indicator of similar effort
across all repetitions during repeated trials (De Ste Croix et al., 2003).
Neurological
Populations
Isokinetic protocols that are similar to those used in adult populations have been
employed in studies of individuals with neurological impairments. The majority are studies of
fatigue in MS in which either isokinetic concentric (Armstrong et al., 1983; Lambert et al., 2001)
or isometric (Surakka et al., 2004) contractions of the knee extensors and flexors were
investigated in comparison with a control population. Lambert et al. (2001) measured total work
and a FI for three sets of 30 repetitions at 180 degrees/second. Total work was determined to be
reliable for the knee flexors and extensors (.80 and .94, respectively) while the FI had low
reliability (.51 and .36, respectively). Armstrong et al. (1983) and Sunnerhagen et al. (1999)
examined FI in individuals with MS and CVA, respectively, with 50 concentric repetitions at
180 degrees/second; however, reliability was not measured. It is of interest to note that even
though higher speeds were employed, the subjects were able to effectively complete the testing,
despite the inherent motor control issues associated with upper motor neuron lesions.
Conclusions
Although no single standardized protocol exists for the assessment of muscle endurance
in either adult, pediatric, or neurological populations, some conclusions can be drawn from the
available literature (See Table A.2 for a list of fatigue protocols). First, utilizing a set number of
repetitions between 25 and 50 appears to be most reliable. Secondly, although 180
degrees/second is the most common speed utilized in the adult population, speeds of 100
degrees/second or less may be more reliable in children with and without CP. However, the
previous limitation of 30 degrees/second in CP, proposed by Van den Berg-Emons et al. (1996),
appears to be unsupported by recent research. For example, the only study to test muscle

(table continued)
119
Table A.2: Isokinetic Endurance Protocols
Author Popu-
lation Age N Protocol Velocity
(deg/s)
Action
Type
Limb
tested Measurement Reliability
De Ste Croix et Children 12.2 30 Reciprocal KF 90 Isokinetic DOM (ICC Test-retest -1wk)
al., 2003 (+0.3) and KE;
50 maximal reps
Concentric -FI (MPT)
-FI (Avg. Work)
-Total Work
KE / KF = .90 / .36
KE / KF = .85 / .54
KE / KF = .95 / .86
Kellis & Kellis, Adol- 13.8 15 Reciprocal KF 60 Isokinetic NR -Joint moment NR
2001 escents (+0.8) and KE;
30 maximal reps
Concentric -EMG
Burdett & Van Adults NR 36 Reciprocal KF 180 Isokinetic DOM (ICC Test-retest)
Swearingen, and KE; 240 Concentric -Total Work KE(180/240) = .98/.87
1987 25 max reps &
the decline of KE
torque to 50% of
maximum
-Work Ratio
-# of reps
KF(180/240) = .91/.83
KE(180/240) = .48/.55
KF(180/240) = .60/.73
KE only = .84/.71
Emery et al., Adults 21 12 Reciprocal KF 60 Isokinetic NR -# of contractions NR
1994 and KE;
torque decline to
50% of
maximum
150 Concentric
&
Eccentric
Felicetti et al.,
1994
Adults 20-30 50 Reciprocal KF
and KE for
180 Isokinetic
Concentric
Both
-# of reps until 20%
(ICC 3 test sessions)
KE / KF = .74 / .70
60seconds decline in PT
-# of reps until 30%
decline in PT
-# of reps until 50%
decline in PT
-Slope
KE / KF = .70 / .69
KE / KF = .77 / .75
KE /KF = .86 / .83
-Total Work KE / KF = .85 / .82

(table continued)
120
Author Popu-
lation Age N Protocol Velocity
(deg/s)
Action
Type
Limb
tested Measurement Reliability
Gleeson & Adults 28.4 10 Reciprocal KF 180 Isokinetic DOM (ICC 3 test sessions x 5
Mercer, 1992 (+3.9) and KE; Concentric days)
30 maximal reps -FI (work) KE / KF = .84 / .49
-Total Work KE / KF = .93 / .88
Manou et al., Adults 27 12 Reciprocal KF 120 Isokinetic DOM (Reliability coefficient
2002 (+3.8) and KE; Concentric test-retest - 5days)
40 maximal reps -FI (work) KE / KF = .90 / .49
-Total Work KE / KF = .92 / .97
-50% fatigue work KE / KF = .89 / .96
-50% fatigue time KE / KF = .88 / .84
-50% fatigue reps KE / KF = .82 / .90
Montgomery et Adults 20-49 32 # of reciprocal 180 Isokinetic R (ICC)
al., 1989 KF and KE Concentric -Total Work KE = .92
contractions -# of reps KE = .55
performed in -FI #1: (reps 1-5 / Work = .67
45seconds reps 21-25)
-FI #2: (1st 5 reps /
MPT = .60
Work = .72
last 5) MPT = .74
Patton et al., Adults 18-24 32 Elbow flexion to 60 Isokinetic NR -# of contractions NR
1978 exhaustion Concentric
Pincivero et al., Adults 22 21 Reciprocal KF 180 Isokinetic DOM (ICC Test-retest -1wk)
1997 (+2.2) and KE; Concentric & -FI (Work) KE = .62-.74
30 maximal reps NDOM KF = .52-.84
-Total Work KE = .88-.90
KF = .91-.95

(table continued)
121
Author Popu-
lation Age N Protocol Velocity
(deg/s)
Action
Type
Limb
tested Measurement Reliability
Pincivero et al., Adults 22 16 Reciprocal KF 180 Isokinetic DOM (ICC Test-retest;1-2wk)
2001 (+1.9) and KE;
30 maximal reps
Concentric &
NDOM
-FI (Work)
-Slope
KE = .26-.82
KE = .78-.82
Pincivero et al., Adults 22 19 Reciprocal KF & 180 Isokinetic DOM -FI (Work) NR
2003 (+3.8) KE; 30 max reps Concentric -Slope
Schwendner et
al., 1995
Adults 20-40 17 Reciprocal KF &
KE until torque
declined to 50%
of maximum
90 Isokinetic
Concentric
DOM
&
NDOM
-Decline in force
output
NR
Thorstensson & Adults 30 10 Consecutive KE; 180 Isokinetic L -FI (MPT) ME = 1.4%
Karlsson, 1976 (+2.0) 50 max reps Concentric
Armstrong et al.,
1983
Multiple
Sclerosis
MS:
~27-57
C:
~29-58
10
20
Consecutive KE;
50 max reps
190 Isokinetic
Concentric
R -FI (PT) NR
Lambert et al., Multiple MS: 39 15 Reciprocal KE 180 Isokinetic DOM MS
MS (ICC) :
2001 Sclerosis (+1.0)
C: 33
(+7.6)
15
and KF; 3 x 30
max reps
Concentric -FI (Work)
-Total Work
Control
-FI (Work)
-Total Work
KE / KF = .36 / .51
KE / KF = .94 / .80
C (ICC):
KE / KF = .58 / .38
KE / KF = .92 / .81
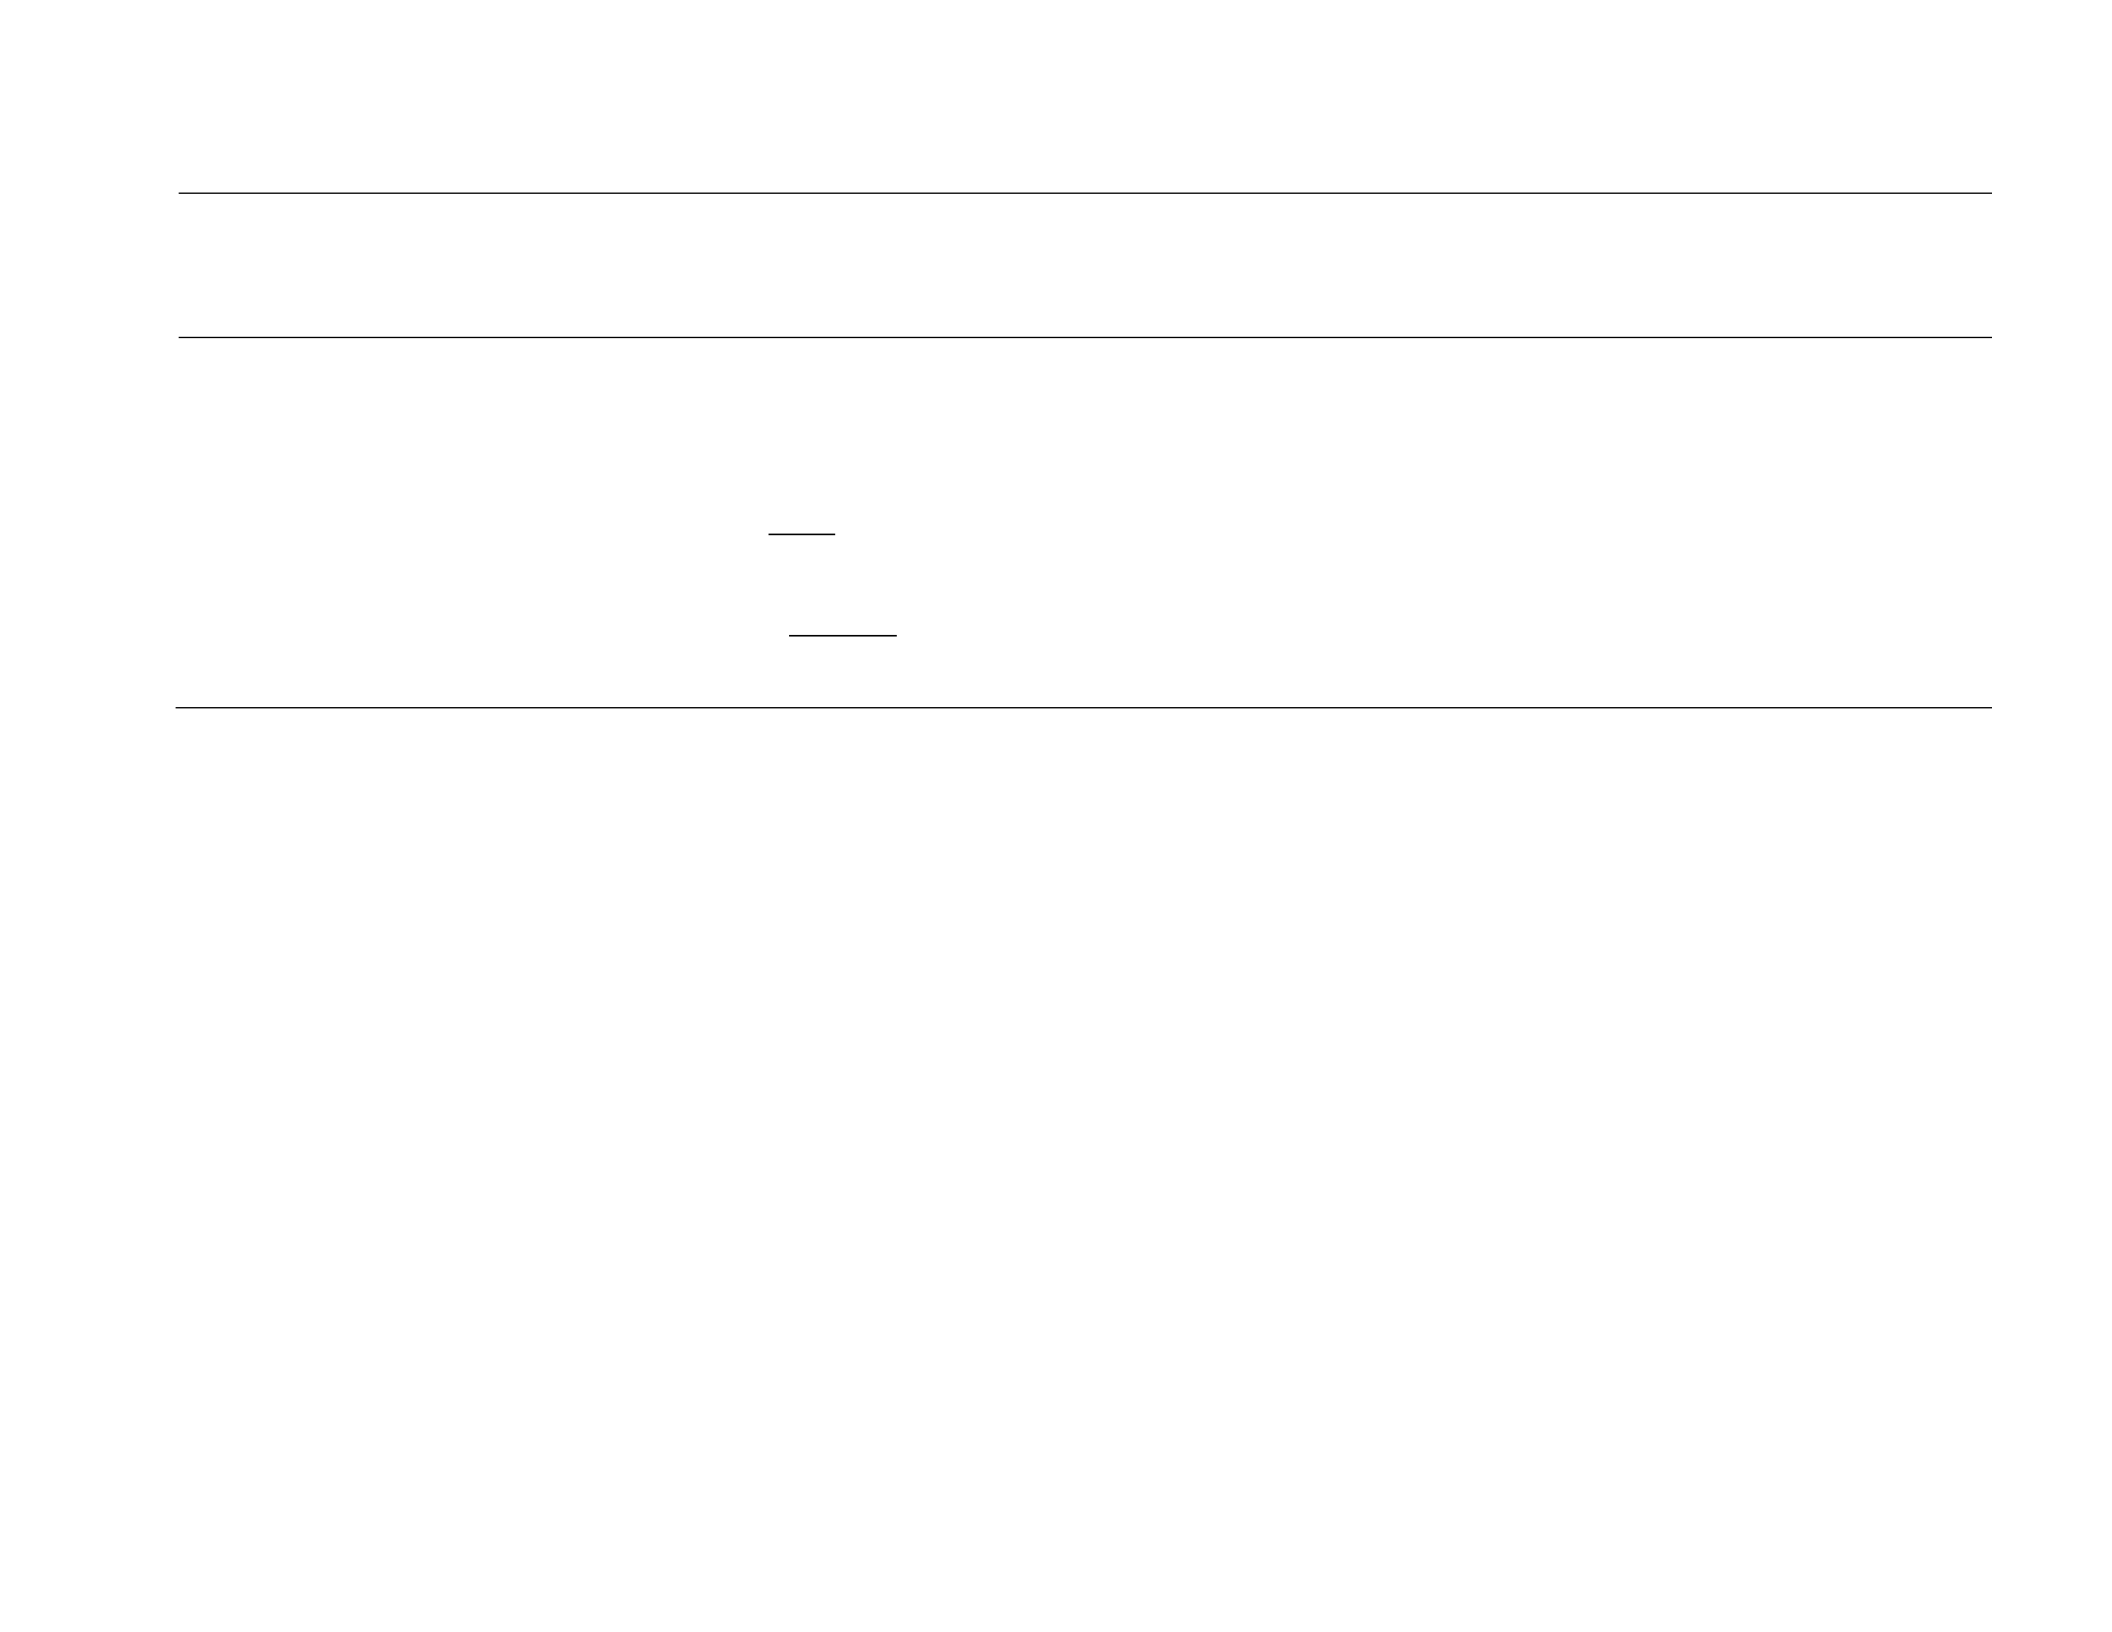
122
Author Popu-
lation Age N Protocol Velocity
(deg/s)
Action
Type
Limb
tested Measurement Reliability
Surraka et al., Multiple 30-54 28 30sec max Isokinetic Both (See ref.) (ICC test-retest -1wk)
2004 Sclerosis isometric
contractions of
KE and KF
Isometric FI#1
FI#2
FI#3
KE / KF = .70 / .85
KE / KF = .68 / .81
KE / KF = .68 / .86
Sunnerhagen et
al., 1999
CVA 40-65 16 Static: 40% max
isometric
contraction
Dynamic: 50 180
Isokinetic
Isometric
Isokinetic
Both Endurance time NR
consecutive KE Concentric FI
NR = not reported; R = right; L = left; DOM = dominant; NDOM = non-dominant; KF = knee flexion; KE = knee extension; FI =
Fatigue index; ICC = Intraclass correlation coefficient; # = number; PT = peak torque; MPT = mean peak torque; ME =
methodological error from duplicate determinations and linear correlation coefficient (r); MS = Multiple Sclerosis; CVA =
Cerebrovascular accident; C = Control; EMG = electromyography

123
endurance in children utilized 90 degrees/second with high reliability and increased comfort
level for the subjects (De Ste Croix et al., 2003). Speeds of 60, 90, and 100 degrees/second have
also been deemed reliable in isokinetic strength testing of children with and without CP (Ayalon
et al., 2000; Deighan et al., 2003; Kellis et al., 1999; Merlini et al., 1995). Third, concentric
repetitions are more reliable than eccentric, especially in children. Lastly, because there is no
consensus on the most reliable measurement of fatigue, several measurements should be made
in order to find the best fit for the data. Furthermore, different parameters should be used to
capture different aspects of the fatigue process, such as the FI, linear slope, and total work.
Conclusion and Hypotheses
Fatigue has been identified as a significant impairment in adolescents and adults with CP
with serious consequences for function and quality of life issues. Further support for the
significance of muscle fatigue in individuals with CP comes from studies of energy expenditure,
morphological and histopathological changes in spastic muscles, and the presence of muscle
fatigue in similar neurological populations (Figure 5).
Despite this evidence, fatigue has not been quantitatively assessed in this population.
Therefore, it is important to specifically define the type of fatigue to be studied (i.e. muscle
fatigue) and to provide an objective measurement that is more scientifically rigorous.
Furthermore, we must understand the contributors to fatigue and their role in the fatigue process.
Future research is needed to address the following aims: 1.) quantification of muscle fatigue in
individuals with CP and in a control group without motor disability, 2.) examination of the
relationships among muscle fatigue and other impairments in order to identify possible
contributors to fatigue, 3.) identification of possible consequences (functional limitations) of
muscle fatigue and the relationship to severity of disease (disability), and 4.) development of
appropriate treatment interventions. Based on the literature presented here regarding the first two

124
aims, the central hypothesis is that 1.) individuals with CP will experience greater levels of
muscle fatigue than those without motor disability and 2.) the amount of fatigue will be related to
other impairments of muscle function, such as weakness, co-contraction, stiffness, and spasticity,
in unique ways.

