



1
IMPACT OF EXERCISE-INDUCED MUSCLE DAMAGE ON HUMAN
PERFORMANCE DURING DYNAMIC EXERCISE
CHAPTER ONE
INTRODUCTION

2
1.1 Introduction
Exercise-induced muscle damage (EIMD) is a commonly experienced phenomenon
resulting from unaccustomed exercise, particularly exercise with a high eccentric
component. Eccentric contractions involve the active lengthening of the muscle and occur
in every day activities such as walking downstairs. Many athletic activities also involve
eccentric muscle action, particularly during the landing or impact phase of running,
jumping or turning. Compared to concentric (shortening) and isometric (static)
contractions, eccentric muscle action is mechanically more efficient but employs a unique
activation strategy which predisposes the muscle to damage (Enoka, 1996; McHugh et al.,
2000).
1.2 Mechanisms of muscle damage
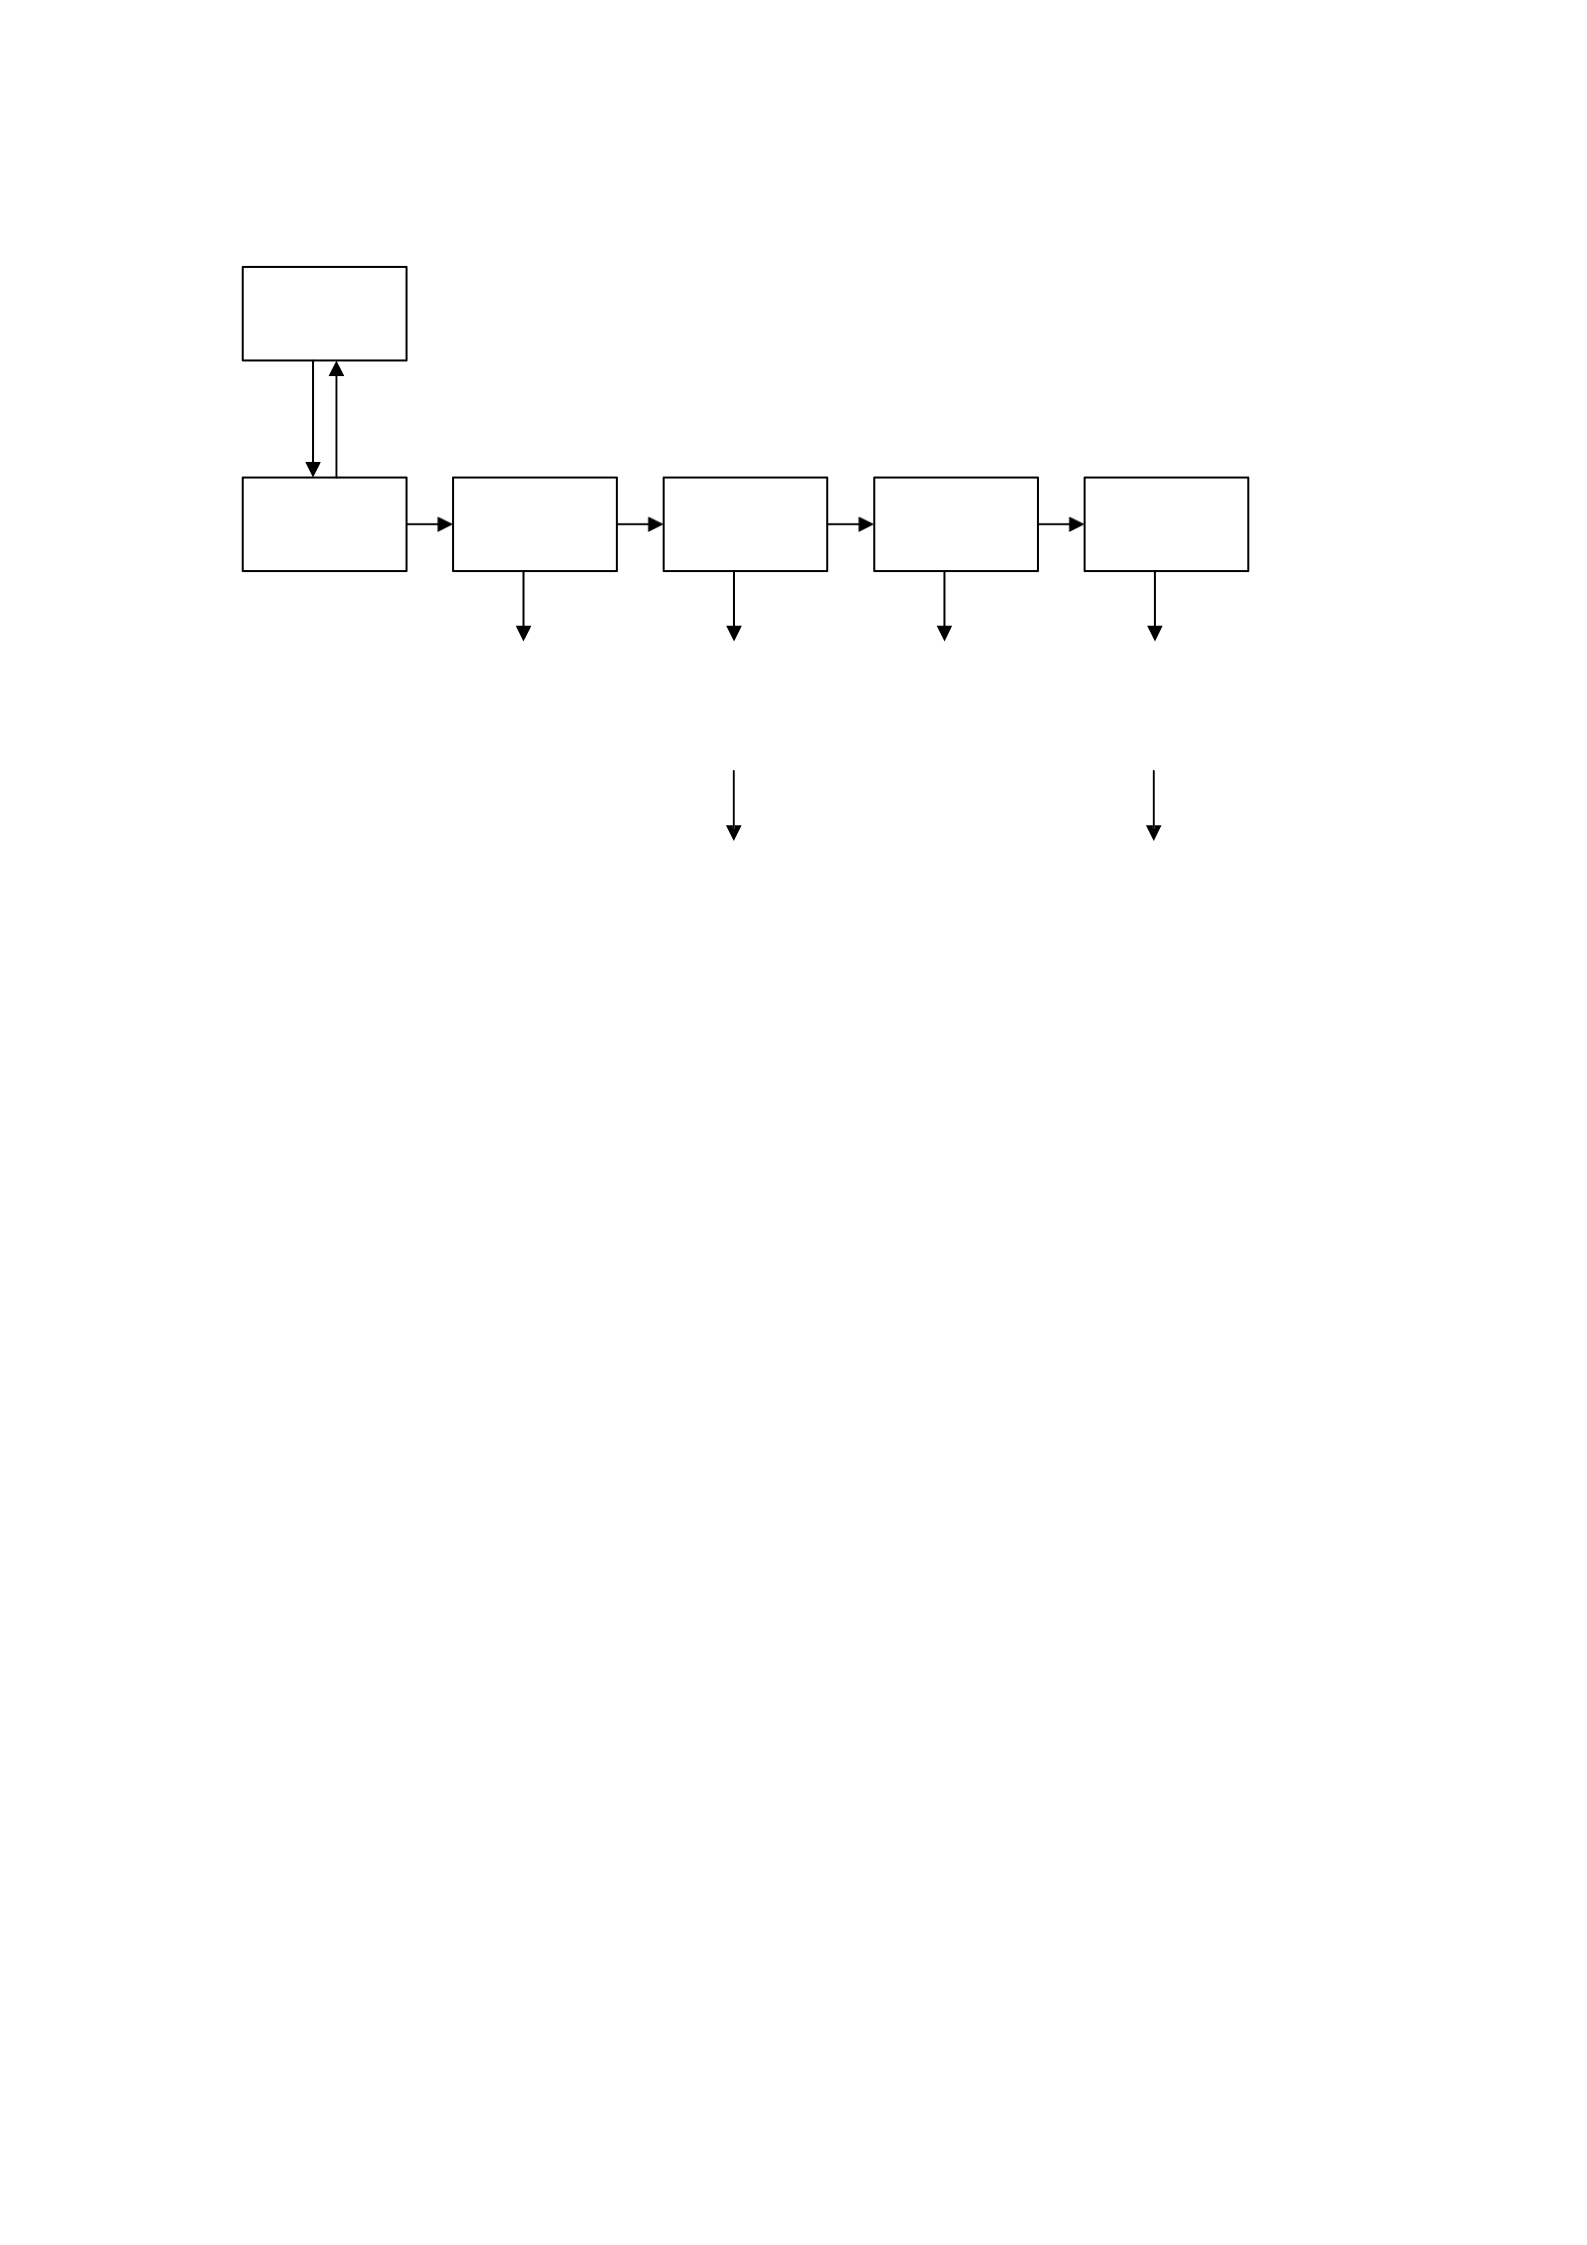
Proske and Morgan (2001) have postulated the initial series of events to explain how
muscle damage results from eccentric exercise (Figure 1.1). The model suggests that
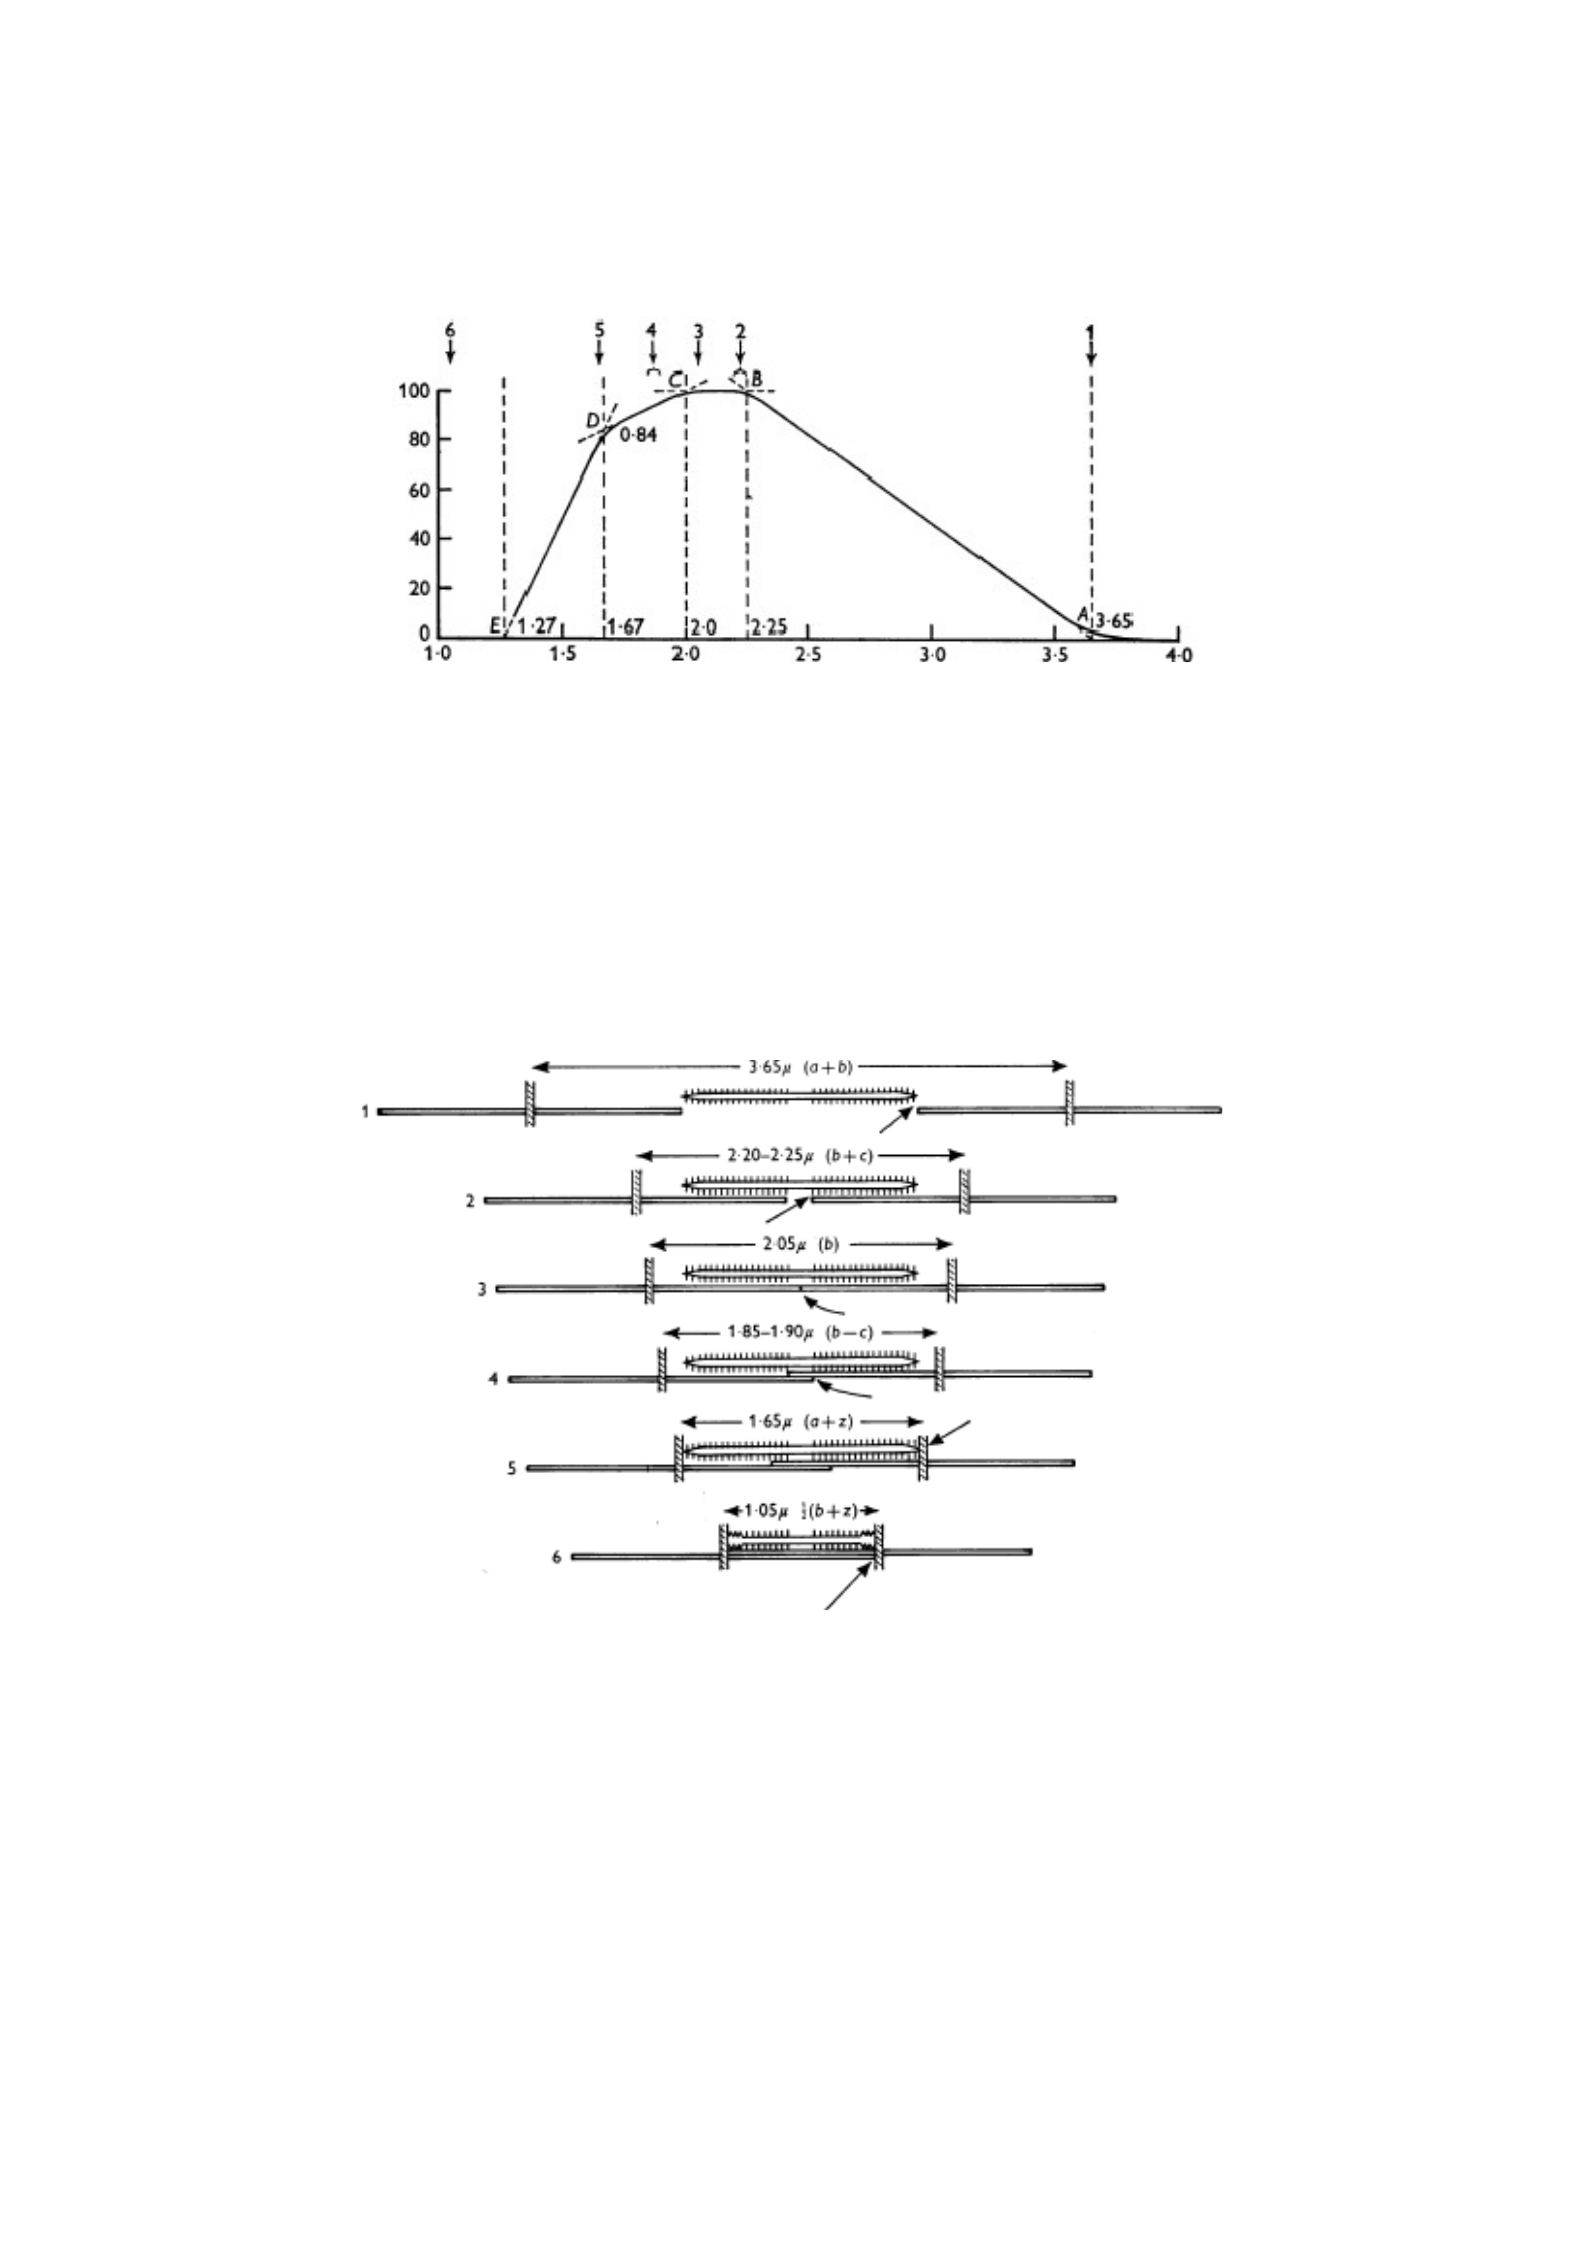
during eccentric contractions weaker sarcomeres are stretched until they are beyond
myofilament overlap. This is understood to occur during the descending limb of the length-
tension curve where non-uniformity in sarcomere length is known to develop (see Figures
1.2 & 1.3) (Gordon et al., 1966). This leads to sarcomere disruption which is then followed
by membrane damage and subsequent dysfunction of the excitation-contraction (E-C)
mechanism. Muscle biopsy data provide evidence of disrupted sarcomeres, including Z-
line streaming (Newham et al., 1983a; Fridén, 1984), and of damage to t-tubules,
sarcoplasmic reticulum and sarcolemma (Lieber et al., 1994, 1996; Fridén & Lieber, 1998).
Disrupted
Sarcomeres
Overstretched
Sarcomeres
Membrane
Damage
Fibre DiesLocal
Contracture
Normal
Sarcomeres
3
Eccentric
Contractions
Shift in Optimum
Length E-C Coupling
Dysfunction
Rise in Passive
Tension
Delayed fall in
Tension
(Non-Reversible)
Fall in Tension
(Reversible) Swelling and
Soreness
Figure 1.1 Postulated series of events leading to muscle damage from eccentric exercise
(Proske & Morgan, 2001, p. 334).
This disruption is reported to occur predominantly in type II fibres, suggesting that they are
preferentially damaged (Fridén et al., 1983; Fridén & Lieber, 1992). More recently,
intravital microscopy observations have also revealed substantial microvascular
dysfunction including an increase in non-red blood cell-flowing capillaries and enlarged
capillary diameters (Kano et al., 2005). These ultrastructural disturbances initiate an influx
of Ca2+ into the sarcoplasm which activates proteolytic pathways involved in muscle fibre
break-down and repair (Peake et al., 2005, Tidball, 2005). These events in turn produce
symptoms associated with muscle damage, including increased intramuscular proteins in
the bloodstream (Hortobágyi & Denahan, 1989), prolonged loss of muscular strength,
decreased range of motion and increased muscle soreness (Clarkson et al., 1992; Cleak &
Eston, 1992).
4
Descending limb
Sarcomere length (μ)
Figure 1.2 The relationship between length and tension in skeletal muscle. Adapted
from Gordon et al. (1966), p.185.
Figure 1.3 Critical stages in the increase of myofilament overlap corresponding to key
points (1–6) labelled on the length-tension curve in figure 2.1. Adapted from Gordon et al.
(1966), p.186.
% maximal tension

5
1.3 Muscle function following eccentric exercise
Although there are several symptoms associated with EIMD, it has been suggested that
measurements of muscle function provide the best means of assessing the magnitude and
duration of muscle injury (Warren et al., 1999). Furthermore, the immediate and prolonged
loss of force-generating capacity that results from eccentric exercise is possibly the most
important symptom when considering the influence of EIMD on the human response to
dynamic exercise (Byrne et al., 2004).
Isometric strength measured at a fixed joint angle is the most frequently used assessment of
muscle function following eccentric exercise (Warren et al., 1999), with the greatest
decrements in maximal voluntary contraction (MVC) occurring immediately after eccentric
exercise, followed by a linear recovery (Byrne et al., 2001). Evaluation of dynamic muscle
function following EIMD can be achieved using isokinetic dynamometry. Although it is
not possible to replicate sport-specific movement patterns and velocities, insights into
dynamic muscle function have been gained using this technique. The magnitude of
strength loss and rate of recovery between isometric, concentric and eccentric muscle
actions appears to be similar following EIMD (Byrne & Eston, 2002a; Michaut et al.,
2002). However, conflicting findings have been reported in relation to changes in peak
torque at different angular velocities. Observations that decrements in peak torque are
greatest at higher angular velocities (Fridén et al., 1983; Eston et al., 1996) support the
notion that type II fibres may be selectively damaged during eccentric exercise (Fridén et
al., 1983; Fridén & Lieber, 1992); but are countered by conflicting evidence that peak
torque is affected to a greater extent at slower rather than faster angular velocities (Gibala
et al., 1995; Deschenes et al., 2000; Michaut et al., 2002).

6
1.4 Dynamic exercise
Athletic performance that relies on the muscle’s ability to generate force rapidly is
negatively impacted following exercise-induced muscle damage (EIMD). The loss of
force-generating capacity results in impaired sprint performances resulting from reductions
in peak power and increases in time to reach peak power. Immediate and prolonged
reductions have been observed in peak power output on a cycle ergometer (Sargeant &
Dolan, 1987; Byrne & Eston, 2002b), in time to peak power (Twist & Eston, 2007) and in
cycle sprint performance (Twist & Eston, 2005). However, recovery is not immediate and
further decrements at 24 and 48 h are observed, suggesting that delayed onset muscle
soreness (DOMS) may influence the dynamic response.
The influence of EIMD on endurance performance remains in dispute. Some studies have
reported no change in sub-maximal running performance following a prior bout of eccentric
muscle-damaging exercise (Hamill et al., 1991; Scott et al., 2003; Paschalis et al., 2005;
Marcora & Bosio, 2007). Whereas other investigations have observed that EIMD has a
negative effect on performance (Braun & Dutto, 2003; Chen et al., 2007b). EIMD does not
appear to alter the V˙
O2
response to sub-maximal cycling (Gleeson et al., 1995, 1998;
Walsh et al., 2001; Moysi et al., 2005; Schneider et al., 2007); however the influence of
EIMD on other cycling performance measures is uncertain.
1.5 Summary
The intention of this thesis is to investigate the effects of exercise-induced muscle damage
(EIMD) on the response to dynamic exercise in human subjects. This topic has been

7
investigated infrequently and findings are equivocal.
Therefore, the main objective is to

E
8
provide empirical evidence to advance the scientific knowledge and understanding of the
phenomenon of EIMD; principally by investigating the physiological, perceived exertion
and metabolic responses to the performance of dynamic exercise with EIMD. This thesis
comprises 4 studies, as outlined below. Studies 1 and 4 used a total sample of 13
participants, 7 of which were common to both studies. Similarly, studies 2 and 3 used a
total sample of 16 participants, 7 of which were common to both studies.
Study 1 The effect of exercise-induced muscle damage on ventilatory and
perceived exertion responses to moderate and severe intensity cycle exercise
This study examined the effect of exercise-induced muscle damage (EIMD) on ventilatory
and perceived exertion responses to cycle exercise. Ten healthy, physically active men
cycled for six minutes at moderate intensity and to exhaustion at severe intensity before and
48 h after eccentric exercise (100 squats with a load corresponding to 70% of body mass).
Changes in ventilation and ratings of perceived exertion (RPE) were calculated for each
individual and expressed against time (moderate and severe exercise) and as a percentage
of time to exhaustion (severe exercise). Ventilation increased during moderate exercise at
48 h ( V˙
; 34.5 ± 5.0 to 36.3 ± 3.8 L.min-1, P<0.05) but increases in RPE were
not
significant.
During severe exercise at 48 h, time to exhaustion (TTE) was reduced and V˙ E
(87.1 ± 14.1 to 93.8 ± 11.7 L.min-1) and RPE (15.5 ± 1.3 to 16.1 ± 1.4) were elevated
(P<0.05). When expressed as a percentage of TTE, the differences in ventilation and RPE
values disappeared. Findings indicate that the augmented ventilatory response to cycle
exercise following EIMD may be an important cue in informing effort perception during
high intensity exercise but not during moderate intensity exercise.

2
9
No change was observed in the blood lactate response, although the ventilatory response
was enhanced, indicating that other ventilatory stimuli may play an important role
following EIMD. The potential dissociation of ventilatory and blood lactate responses
during ramp incremental cycling following EIMD was investigated in study 2.
This study has formed the basis of the following publication:
Davies, R. C., Rowlands, A. V., & Eston, R. G. (2009). Effect of exercise-induced muscle
damage on ventilatory and perceived exertion responses to moderate and severe intensity
cycle exercise. European Journal of Applied Physiology, 107(1), 11-19.
Study 2 The effect of eccentric exercise-induced muscle damage on the gas
exchange threshold
A prior bout of eccentric muscle-damaging exercise augments the ventilatory response to
constant-load cycle exercise without altering the blood lactate profile. However, the
influence of exercise-induced muscle damage (EIMD) on the performance of ramp
incremental exercise has received sparse attention. This study tested the hypothesis that
EIMD would augment the ventilatory response to subsequent ramp incremental cycle
exercise leading to a reduction in the gas exchange threshold (GET). In the absence of an
altered blood lactate profile this would indicate a dissociation of the GET from the lactate
threshold. Ten healthy, physically active male subjects (age, 25 ± 7 years; mass, 80.1 ±9.9
kg; height, 1.80 ± 0.08 m) performed maximal incremental cycle exercise tests before (pre)
and 48 h after (post) completing 100 squats, with a load corresponding to 70% body mass.
Following eccentric exercise GET occurred earlier (pre GET V˙ O2 : 1.58 ± 0.26; post
GET
V˙ O : 1.41 ± 0.14 l.min-1) while the blood lactate response was unchanged (P > 0.05). The
dissociation between GET and the blood lactate response during cycling with EIMD
indicates that the two phenomena are not causally linked. We propose that the 13%

10
increase in ventilation and resultant reduction in GET are evoked predominantly by

11
increased activation of group III and IV afferents which are stimulated via the mechanical
disruption of muscle fibres and local microvasculature due to eccentric exercise.
The decreased endurance capacity observed may have resulted from a shift in the muscle
metabolic profile to an increased reliance on non-oxidative metabolism. Therefore, the
purpose of study 3 was to investigate alterations in muscle metabolism during incremental
exercise to exhaustion.
This study is currently under review for publication:
Davies R.C., Rowlands A.V., Poole D.C., Jones A.M. and Eston R.G. Exercise-induced
muscle damage dissociates the Lactate and Gas exchange thresholds. Currently under
review.
Study 3 The 31P-MRS metabolic response to incremental exercise following
eccentric, muscle-damaging exercise
Performance decrements associated with EIMD include a reduction in maximal force-
generating capacity (Clarkson et al., 1992) and a shorter time to exhaustion (Asp et al.,
1998; Carmichael et al., 2005, 2006). Asp et al. (1998) have proposed that EIMD results in
a shift to more glycolytic energy production which may contribute to the accelerated
development of fatigue. This study investigated the influence of EIMD on changes in
muscle metabolism during incremental exercise using 31phosphorus magnetic resonance
spectroscopy (31P-MRS). Before and 48 h after performing100 squats, 31P-MRS was used
to measure dynamic changes in [PCr], [Pi], [ADP] and pH during knee-extensor
incremental tests to exhaustion. The resting [Pi]:[PCr] ratio was increased 48 h after
eccentric exercise (pre: 0.12 ± 0.02; post: 0.18 ± 0.05). During incremental exercise the
changes in pH, [PCr] and [Pi]:[PCr] were similar but did not continue for as long. Time to
exhaustion and associated peak work rate values were significantly reduced following
eccentric exercise (pre: 519 ± 56; post: 459 ± 63 s) and (pre: 29 ± 4; post: 25 ± 4 W),

12
respectively. End exercise pH and [PCr] values were significantly higher (pre: 6.75 ± 0.12;
post: 6.83 ± 0.15) and (pre: 20 ± 13; post: 33 ± 15 % baseline values), respectively. These
findings demonstrated that the accelerated development of fatigue following eccentric
exercise did not result from alterations in muscle phosphate metabolism.
While phosphate metabolism does not appear to have a detrimental influence on the
performance of dynamic exercise, the substantial microvascular dysfunction observed
following EIMD (Kano et al., 2005) may contribute to impaired performance due to
disruptions to delivery and distribution of O2 within the capillary bed of the active muscle.
Thus study 4 was designed to investigate the influence of EIMD on the matching of O2
delivery to O2 utilisation.
This study is currently under review for publication:
Davies RC, Eston RG, Fulford J, Rowlands AV and Jones AM. Muscle damage alters the
metabolic response to dynamic exercise in humans: a 31P-MRS study. Currently under
review.
Study 4 The effect of eccentric exercise-induced muscle damage on the
dynamics of muscle oxygenation and pulmonary oxygen uptake
Unaccustomed eccentric exercise has a profound impact on muscle structure and function.
However, it is not known whether associated microvascular dysfunction disrupts the
matching of
O2 delivery ( Q˙ O2 ) to O2 utilisation ( V˙ O2 ). Near infra-red spectroscopy
(NIRS) was used to test the hypothesis that eccentric exercise-induced muscle damage
would
elevate
the
muscle Q˙ O2 : V˙ O2 ratio
during
severe
intensity exercise
whilst
preserving the speed of the V˙ O2 kinetics at exercise onset. Nine physically active men
completed ‘step’ tests to severe-intensity exercise from an unloaded baseline on a cycle

13
ergometer before and 48 h after eccentric exercise (100 squats with a load corresponding to
70%
of
body mass).
NIRS
and
breath-by-breath
pulmonary V˙ O2 were measured
continuously during the exercise tests and subsequently modelled using standard non-linear
regression
techniques. There
were
no
changes
in
phase
II pulmonary V˙ O2 kinetics
following the onset of exercise (time constant, pre: 25 ± 4; post: 24 ± 2 s; amplitude, pre:
2.36 ± 0.23; post: 2.37 ± 0.23 L/min; all P>0.05). However, the primary (pre: 14 ± 3; post:
19 ± 3 s) and overall (pre: 16 ± 4; post: 21 ± 4 s) mean response time of the [HHb] response
was significantly slower following eccentric exercise (P<0.05). The slower [HHb] kinetics
observed following eccentric exercise is consistent with an increased
Q˙ O2 : V˙ O2 ratio
during transitions to severe-intensity exercise. We propose that unchanged primary phase
V˙ O2 kinetics are associated with an elevated Q˙ O2 : V˙ O2 ratio that preserves blood-
myocyte O2 flux.
This study has formed the basis of the following publications/presentations:
Publication:
Davies, R. C., Eston, R. G., Poole, D. C., Rowlands, A. V., Dimenna, F., Wilkerson, D. P.,
et al. (2008). The effect of eccentric exercise-induced muscle damage on the dynamics of
muscle oxygenation and pulmonary oxygen uptake. Journal of Applied Physiology, 105(5),
1387-1388.
Because the reviewers thought the paper could have substantial impact on the field, Dr.
Mark Burnley was invited to write a Commentary to accompany the publication of the
article:
Burnley M. (2008). Found in translation: the dependence of oxygen uptake kinetics on O 2
delivery and O2 utilization. Journal of Applied Physiology, 105(5), 1387-1388
Presentation
Davies R, Eston R, Poole D, Rowlands A, Dimenna F, Wilkerson D, Twist C, and Jones A.
(2008). The influence of exercise-induced muscle damage on pulmonary oxygen uptake
and muscle deoxygenation kinetics during high intensity exercise. In J. Cabri, F. Alves, D.
Araujo, J. Barreiros and A. Veloso (Eds), 13th Annual Congress of the European Congress
of Sports Sciences, Book of Abstracts (p630). Estoril.

14
CHAPTER TWO
REVIEW OF THE LITERATURE

15
2.1 Introduction
The temporary damage to skeletal muscle that results from unaccustomed exercise has been
the subject of investigation by exercise physiologists for over 100 years. In 1902 Hough
described the delayed but transient soreness experienced when untrained muscle made a
series of contractions against a strong spring, suggesting that it resulted from ruptures
within the muscle. Since then, several hundred published investigations have attempted to
elucidate the underlying mechanisms of this phenomenon and document its symptoms.
Direct histological analysis of both human and animal muscle tissue has provided evidence
to support Hough’s (1902) original contention that changes in skeletal muscle morphology
are symptomatic of unaccustomed exercise.
2.2 Changes in skeletal muscle morphology
Human muscle biopsy data has provided direct evidence of considerable disruption in the
ultrastructure of skeletal muscle following unaccustomed eccentric exercise (Fridén et al.,
1981, 1983; Fridén, 1984; Newham et al., 1983a; Jones et al., 1986; Gibala et al., 1995).
Disturbances which originate in the myofibrilar Z-band are seen as streaming, broadening
or total disruption. Z-line disruption is the most frequently reported ultrastructural
abnormality and as such may represent the weak link in the myofibril contractile
mechanism (Newham et al., 1983a; Fridén 1984). Reports of greater disruption of type II
fibres have led to the understanding that these fibres are preferentially damaged during
eccentric exercise (Fridén et al., 1983; Fridén , 1984; Jones et al., 1986 Lieber et al., 1991;
MacPherson et al., 1996). Eccentric contractions are understood to generate higher levels
of mechanical stress than concentric or isometric contraction due to reduced motor unit
activation (Enoka, 1996; Armstrong et al., 1991; McHugh et al., 2000).
This has led to

B
16
speculation that type II motor units are selectively recruited during eccentric contraction
(Enoka, 1996; McHugh et al., 2000, 2002; Nardone & Schieppati, 1988; Nardone et al.,
1989; Howell et al., 1995) and that the excessive stress on the small number of active fibres
leads to them becoming damaged (McHugh et al., 2000).
Figure 2.1
Longitudinal sections of fast-twitch (FT) fibres in A) triceps brachii muscle
of a sedentary control rat, and B) rat triceps brachii muscle 1 day after exercise downhill
running (DH). Scale bars, 1μm. Adapted from Takekura et al. (2001). Note the Z-line
smearing and focal disruption of the A-band region following downhill running.
In animal models used to study EIMD, damage to contractile and cytoskeletal components
of predominantly type II fibres has been revealed using histological staining (Fridén and
Lieber, 1992; Takekura et al., 2001) (Figure 2.1). Lack of staining for cytoskeletal proteins
has provided evidence of disruption to the sarcolemma and cytoskeleton (Lieber et al.,
1994, 1996; Fridén & Lieber, 1998; Komulainen et al., 1998, 1999, 2000). Morphological
changes in skeletal muscle also include ultrastructural changes in the arrangement of the T-
tubules which is believed to occur when adjacent myofilaments show disparate degrees of
stretch (Takekura et al., 2001; Yueng et al., 2002), and the presence of multiple central

17
nuclei (Kano et al., 2004). Furthermore, disruption of capillary geometry including
enlarged capillary diameters has been observed using intravital microscopy, possibly
resultant to myocyte swelling (Kano et al., 2004).
In human studies changes in the intermediate filament system have been interpreted as
evidence of myofibrillar and cytoskeletal damage (Fridén et al., 1984). However, this
interpretation has been challenged by Yu and colleagues (2002) who have reported
increased rather than decreased staining of cytoskeletal proteins. These authors suggested
that their findings provide evidence of muscle repair and remodelling rather than muscle
damage from eccentric contraction (Yu et al., 2002, Yu & Thornell, 2002). Whilst animal
models may not always accurately reflect changes in their human counterparts, they have
provided valuable insights which are not so easily procured in human models. Indeed,
caution should be taken when interpreting the results of studies using human muscle biopsy
as there is evidence to suggest that the biopsy procedure itself may produce some changes
mistakenly attributed to EIMD (Malm et al., 2000; Roth et al., 2000). Nonetheless direct
analysis of muscle tissue has revealed substantial disruption in both human and animal
models of EIMD.
2.3 Indirect markers of muscle damage
Due to the invasive nature of muscle biopsy procedures in human investigations research
scientists have increasingly selected to utilise indirect markers of muscle damage in an
attempt to further our understanding of the underlying mechanisms of EIMD and its
symptoms.

18
2.3.1 Muscle protein efflux
The structural and functional status of muscle tissue can be determined by the level of
skeletal muscle enzymes in the blood. If sarcolemmal integrity is compromised as a result
of eccentric exercise (as reported in 2.2), an efflux of muscle proteins into the bloodstream
will result (Hortobágyi & Denahan, 1989). Muscle proteins such as creatine kinase (CK)
and lactate dehydrogenase (LDH) are commonly used as indirect markers of muscle
damage. In fact, Warren et al. (1999) reported that, of human studies reviewed, over 50%
used changes in blood levels of myofibre proteins as evidence of EIMD with CK being the
most frequently reported. However, the time course of CK activity in the blood appears to
be dependant on the damage protocol employed. Following muscle-damaging exercise
such as downhill running, weightlifting or plyometric exercise, plasma CK levels peak at
24-48 h (Paul et al., 1989; Eston et al., 1996; Horita et al., 1999; Byrne and Eston, 2002a;
Twist & Eston, 2005; Chen et al., 2007b). In contrast, high-force eccentric exercise using
isokinetic dynamometers induces a delayed response with CK levels peaking at day 4-5
(Clarkson et al., 1992; Nosaka & Clarkson, 1992, Chen et al., 2003, Zainuddin et al., 2005).
Interpretation of the CK response to eccentric exercise is further complicated by high inter-
subject variability despite similar decrements in contractile function (Clarkson and
Ebbeling, 1988; Hortobágyi and Denahan, 1989). Whilst it is compelling to hypothesise a
relationship between the loss of sarcolemmal integrity, increase in plasma CK activity and
loss of muscle function, there is no evidence that plasma CK levels accurately reflect the
extent of myofibre damage caused (Nosaka & Clarkson, 1992).

19
2.3.2 Calcium homeostasis
Myofibril damage in animal models of EIMD has been associated with the loss in calcium
(Ca2+) homeostasis due to disturbances of the myocyte membrane (Armstrong, 1990). The
disruption of sarcoplasmic reticulum (SR) (Byrd, 1992; Fridén & Lieber, 1996) increases
membrane permeability and is understood to be responsible for increases in intracellular
Ca2+ concentration (Armstrong, 1984). Increases in Ca2+ may then contribute to the further
degradation of the muscle tissue by stimulating the release of calcium-activated neutral
proteases such as calpain which have been shown to damage Z-line-associated proteins
(Busch et al., 1972; Belcastro, 1993; Belcastro et al., 1998). However, the direct
investigation of SR regulation of calcium in human EIMD is extremely limited and has
produced conflicting results. Nielson et al. (2005) observed no change in SR function
following eccentric, muscle-damaging exercise. In contrast, Enns and colleagues (1999)
reported no immediate change in SR Ca2+ uptake but a prolonged alteration in SR function
in the 2-14 day recovery period. The administration of calcium channel blockers (CCB) in
animal models of EIMD has been reported to reduce or prevent the rise in intracellular Ca2+
and subsequent injury (Soza et al., 1986; Duan et al., 1990; Duarte et al., 1992; Armstrong
et al., 1993). Similarly, in humans, damage to some sarcomeric proteins was attenuated or
delayed by the administration of CCBs following eccentric exercise (Beaton et al., 2002).
However, the administration of CCBs unexpectedly increased the infiltration of
inflammatory cells including neutrophils and macrophages into the muscle tissue, possibly
due to the influence of CCBs on vascular and smooth muscle tone (Beaton et al., 2002).

20
2.3.3 Inflammatory response
Following eccentric, muscle-damaging exercise, inflammatory cells such as neutrophils and
macrophages are understood to infiltrate the muscle in order to remove necrotic tissue and
initiate the process of muscle repair and regeneration (MacIntyre et al., 1995; Peake et al.,
2005; Tidball, 2005). The infiltration of these inflammatory cells has also been implicated
in producing secondary cytoskeletal disruptions to eccentrically exercised muscle (Pizza et
al., 2001, 2005)
The first inflammatory cells to accumulate are neutrophils (Fielding et al., 1993; Malm et
al., 2000). These cells remove necrotic tissue by phagocytosis and release cytokines to
attract additional inflammatory cells. Neutrophils can permeate human skeletal muscle
within an hour of eccentric exercise and remain present for up to 5 days (Fielding et al.,
1993) although significant increases are more commonly reported to last up to 24 h
(MacIntyre et al., 1996, 2000, 2001, Beaton et al., 2002). Neutrophil accumulation is
understood to activate resident macrophages and attract further macrophage invasion.
Macrophages are not only actively phagocytic but may also promote repair and
regeneration via the release of cytokines known to cause myoblast proliferation in vitro
(Hawke & Garry, 2001). However, a recent review has revealed that only 55% of human
studies, as opposed to 85% of animal studies, have detected neutrophil infiltration in
exercise-damaged muscle (Schneider & Tiidus, 2007). Animal models of EIMD are most
commonly used to study inflammatory cell accumulation due to the difficulties inherent in
multiple biopsy procedure in human subjects (Pizza et al., 2008). Thus the inflammatory
response to eccentric exercise in humans remains controversial, not least because it appears
to be dependent on a wide variety of factors including the mode, intensity and duration of

21
exercise, the muscle groups examined and the method of detection (directly using muscle
biopsy or indirectly via blood analysis) (Peake et al., 2005; Tidball, 2005; Schneider &
Tiidus, 2007).
2.3.4 Impaired metabolism
A number of studies have indicated that intramuscular glycogen stores are depleted
following eccentric, muscle damaging exercise. O’Reilly et al. (1987) demonstrated a
prolonged depletion of muscle glycogen content following 45 min of eccentric cycling.
Muscle biopsy samples showed that muscle glycogen content had dropped to 61% of
baseline values immediately after eccentric exercise and were further depleted to 44% of
baseline values 10 days after the exercise bout. Subsequent studies have corroborated these
findings which indicate that EIMD may impair muscle glycogen resynthesis (Asp et al.,
1995; Asp et al., 1998; Costill et al., 1990).
Resting muscle glycogen uptake is decreased following eccentric exercise due to a decrease
in insulin sensitivity. The transient insulin resistance reported following eccentric exercise
(Kirwan et al., 1992; del Aguila et al., 2000; Asp et al., 1996) has been linked to the
decrease in a major glucose transport protein, GLUT-4 (Asp et al., 1995; Asp et al., 1996).
The translocation of GLUT-4 to the cell membrane when additional glucose is required is
initiated by the binding of insulin to membrane-bound insulin receptors (IRS-1) (Tee et al.,
2007). The physiological stress associated with EIMD appears to impair the insulin
stimulation of IRS-1 and the subsequent activation of GLUT-4, leading to decreased
insulin-mediated glucose uptake (del Aguila et al., 2000).

22
While type I muscle fibres are predominantly oxidative, type II fibres, which are selectively
recruited (Enoka, 1996; McHugh et al., 2000, 2002; Nardone & Schieppati, 1988; Nardone
et al., 1989; Howell et al., 1995) and preferentially damaged (Fridén et al., 1983; Fridén ,
1984; Jones et al., 1986 Lieber et al., 1991; MacPherson et al., 1996) during eccentric
contractions, are predominantly glycolytic. Asp et al. (1998) have reported that the resting
glycogen content of type II fibres is more severely depleted than that of type I fibres
following eccentric exercise (Asp et al., 1998). This observation has led to speculation that
increased glygogenolysis may result from EIMD and could also be responsible for the
higher resting blood lactate concentration [La] reported with EIMD (Asp et al., 1996, Asp
et al., 1998). Elevated [La] has also been reported during exercise with EIMD and has
similarly been attributed to a shift to more glycolytic energy production (Braun & Dutto,
2003; Chen at al., 2007b, 2008; Gleeson et al., 1995, 1998). It has been suggested that
damage to type II fibres would necessitate a greater recruitment of these fibres during
exercise with EIMD in order to maintain the required force production (Gleeson et al.,
1998). However, higher [La] does not appear to be an obligatory consequence of EIMD.
Several studies have reported no change in the [La] response to exercise following prior
eccentric exercise (Hamill et al., 1991; Scott et al., 2003; Marcora & Bosio, 2007; Moysi et
al., 2005). A recent study by Schneider et al. (2007) reported unchanged phase II V˙ O2
kinetics indicating that EIMD did not compromise oxidative function. These authors
suggested that the increase in [La] observed must therefore result from an increased lactate
efflux from the active muscle due to increased membrane permeability following muscle-
damaging exercise (Schneider et al., 2007).

23
2.3.5 Delayed onset muscle soreness
Delayed onset muscle soreness (DOMS) was first described by Hough (1902) and is the
characteristic manifestation most commonly associated with EIMD. In a review of
measurement tools used to assess EIMD, Warren et al. (1999) reported that subjective and
objective assessment of DOMS was reported in 63% and 12% of the human studies
reviewed, respectively; the most frequently observed measurement of muscle damage
employed (Warren et al., 1999). However, a poor temporal relationship exists between
DOMS and changes in muscle morphology (Newham et al., 1983a; Jones et al., 1986) and
changes in muscle function (Newham et al., 1983b; Howell et al., 1993; Rodenburg et al.,
1993; Saxton et al., 1995; Prasartwuth et al., 2005). The ‘delay’ in the experience of
soreness appears to vary amongst individuals but peak soreness generally develops between
24 and 48 h after the muscle-damaging exercise (Newham et al., 1983b, 1988; Jones et al.,
1987, 1989; Clarkson et al., 1992; Cleak & Eston, 1992) and gradually subsides, usually
disappearing within 96 h (Jones et al., 1987; Cleak & Eston 1992). In contrast, changes in
muscle morphology were found immediately after completion of a 20 min step-test with the
severity of the damage increasing in the biopsy samples taken at 24 and 48 hours (Newham
et al., 1983a). In an earlier investigation Fridén and colleagues (1981) demonstrated that
ultrastructural disturbances were 3 times greater in biopsy samples taken 2 as opposed to 7
days after the eccentric exercise bout although no biopsy was taken immediately after the
damage protocol which involved repeatedly running downstairs (Fridén et al., 1981).
Functional impairments, in particular changes in strength also follow a different time
course to the development of DOMS (Rodenburg et al., 1993; Newham et al., 1983b:
Nosaka et al., 2002). Strength decrements are greatest immediately after eccentric exercise
and demonstrate a linear recovery back to baseline measurements (Clarkson et al., 1992;

24
Sayers & Clarkson, 2001; Howell et al., 1993; Byrne & Eston, 2002a) usually within 5-7
days (Armstrong, 1984; Clarkson & Tremblay 1988) although in some individuals,
recovery may take up to several weeks (Clarkson et al., 1992; Howell et al., 1993). Thus
DOMS is a poor indicator of both functional impairment and the magnitude of
morphological muscle damage.
Several theories have been proposed to explain the mechanisms responsible for the
sensation of DOMS, including the muscle damage theory originally presented by Hough
over 100 years ago (Hough, 1902). The mechanical disruption of structural elements, (for
further detail see section 2.2) is believed to contribute to the stimulation of pain receptors
(nociceptors). These are primarily group III and IV thin-fibre afferent neurons, located in
the muscle, connective tissue, musculotendinous junction, arterioles and capillaries and
their stimulation is understood to lead to the sensation of pain (Cheung et al., 2003).
Several studies have demonstrated a relationship between increases in muscle soreness and
impairments in dynamic muscle function (Horita et al., 1999; Proske et al., 2003;
Weerokkody et al., 2003b). However, as explained above, differences in the temporal
relationship between DOMS and mechanical disruption indicate that the muscle damage
theory can only partially explain the development of DOMS. The noxious stimulus of
lactic acid has been implicated in producing the sensation of DOMS (Armstrong, 1984).
Elevations in blood lactate concentration [La] have been reported in several studies during
exercise following EIMD (Gleeson et al., 1995, 1998; Braun & Dutto, 2003). However, the
lactic acid theory has largely been rejected as there appears to be no relationship between
ratings of soreness and blood [La] levels following a bout of downhill running designed to

25
induce EIMD (Schwane et al., 1983) and higher levels of lactate have been shown not to
induce soreness in concentric exercise (Armstrong, 1984; Schwane et al., 1983).
Inflammation and swelling triggered by the damage is presently the most widely accepted
proposed mechanism for DOMS (Smith, 1991, Proske & Morgan, 2001; Cheung et al.,
2003). The pain or soreness resulting from eccentric exercise manifests itself as a dull
aching pain that is stimulated by either palpation or contraction and is not present at rest
(Cleak & Eston, 1992; Avela et al., 1999; Komi, 2000). Several studies have proposed that
swelling subsequent to EIMD may be mechanistically implicated in the development of
DOMS due to increases in local tissue pressure (Howell et al., 1985; Bobbert et al., 1986;
Fridén et al., 1986). Smith (1991) has hypothesised that increases in intramuscular pressure
during contraction or palpation would provide sufficient mechanical stimulus for the
sensitisation of mechanical nociceptors (Smith, 1991). These thin-fibre afferents are also
known to be sensitised by various inflammatory mediators including bradykinins,
prostaglandins and histamines which are released during the process of proteolytic
breakdown and repair (Clarkson & Hubal, 2002). It has been suggested that the delay in
the inflammatory response may account for the delay in the symptoms of DOMS (Smith,
1991). However, Taguchi and colleagues (2005) have demonstrated that chemical stimuli
including pH 5.5, adenosine triphosphate, and bradykinin, do not influence the response of
group III and IV muscle afferents to eccentric exercise (Taguchi et al., 2005).
2.3.6 Changes in strength
The immediate and prolonged loss of strength that occurs after eccentric exercise is one of
the most frequently used markers of EIMD. In a review of measurement tools used in

26
studies of EIMD, Warren et al. (1999) reported that 50% of human studies measured
maximal voluntary contraction (MVC) torque, a measure which the authors suggest
provides the most accurate and reliable indirect marker of muscle damage in human studies
(Warren et al., 1999). An immediate loss of force generating capacity may also be
observed following non-damaging concentric exercise but recovery to baseline strength
occurs within hours (Newham et al., 1983b; Jones et al., 1989). The greatest strength loss
and longest recovery times have been associated with high-force eccentric protocols such as
that employed by Newham and colleagues (1987) which involved maximal eccentric
contraction of the elbow flexors. These authors and others have reported strength
decrements of over 50% compared to pre-exercise values, with a linear recovery to baseline
typically lasting 1 - 2 weeks (Newham et al., 1987; Saxton et al., 1995; Nosaka et al., 1991)
although in some individuals, recovery may take up to several weeks (Clarkson et al., 1992;
Howell et al., 1993). In contrast, downhill running (Eston et al., 1996, Eston et al., 2000)
and bar-bell squatting protocols (Byrne & Eston 2002a, 2002b; Moysi et al., 2005)
designed to provoke muscle damage, typically generate a more modest loss in force-
generating capacity with strength decrements of between 10 and 30% and recovery to
baseline occurring within 4-7 days.
2.4 Muscle function following exercise-induced muscle damage
Morgan and Allen (1999) proposed that the earliest events in eccentric, muscle-damaging
exercise involve the over-stretching of randomly distributed sarcomeres, although the initial
decline in strength may be attributed to metabolic fatigue, damaged muscle or a
combination of both (Morgan & Allen 1999). If sarcomeres are stretched to a point of
minimal overlap between actin and myosin filaments, cross-bridge formation would be

27
reduced and the ability to generate force would be compromised (Clarkson et al., 1992). In
support of this hypothesis, it has been reported that loss in strength is greater when the
damaging exercise is performed with muscle at longer rather than shorter lengths (Newham
et al., 1988; Child et al., 1998).
2.4.1 Changes in optimal muscle length
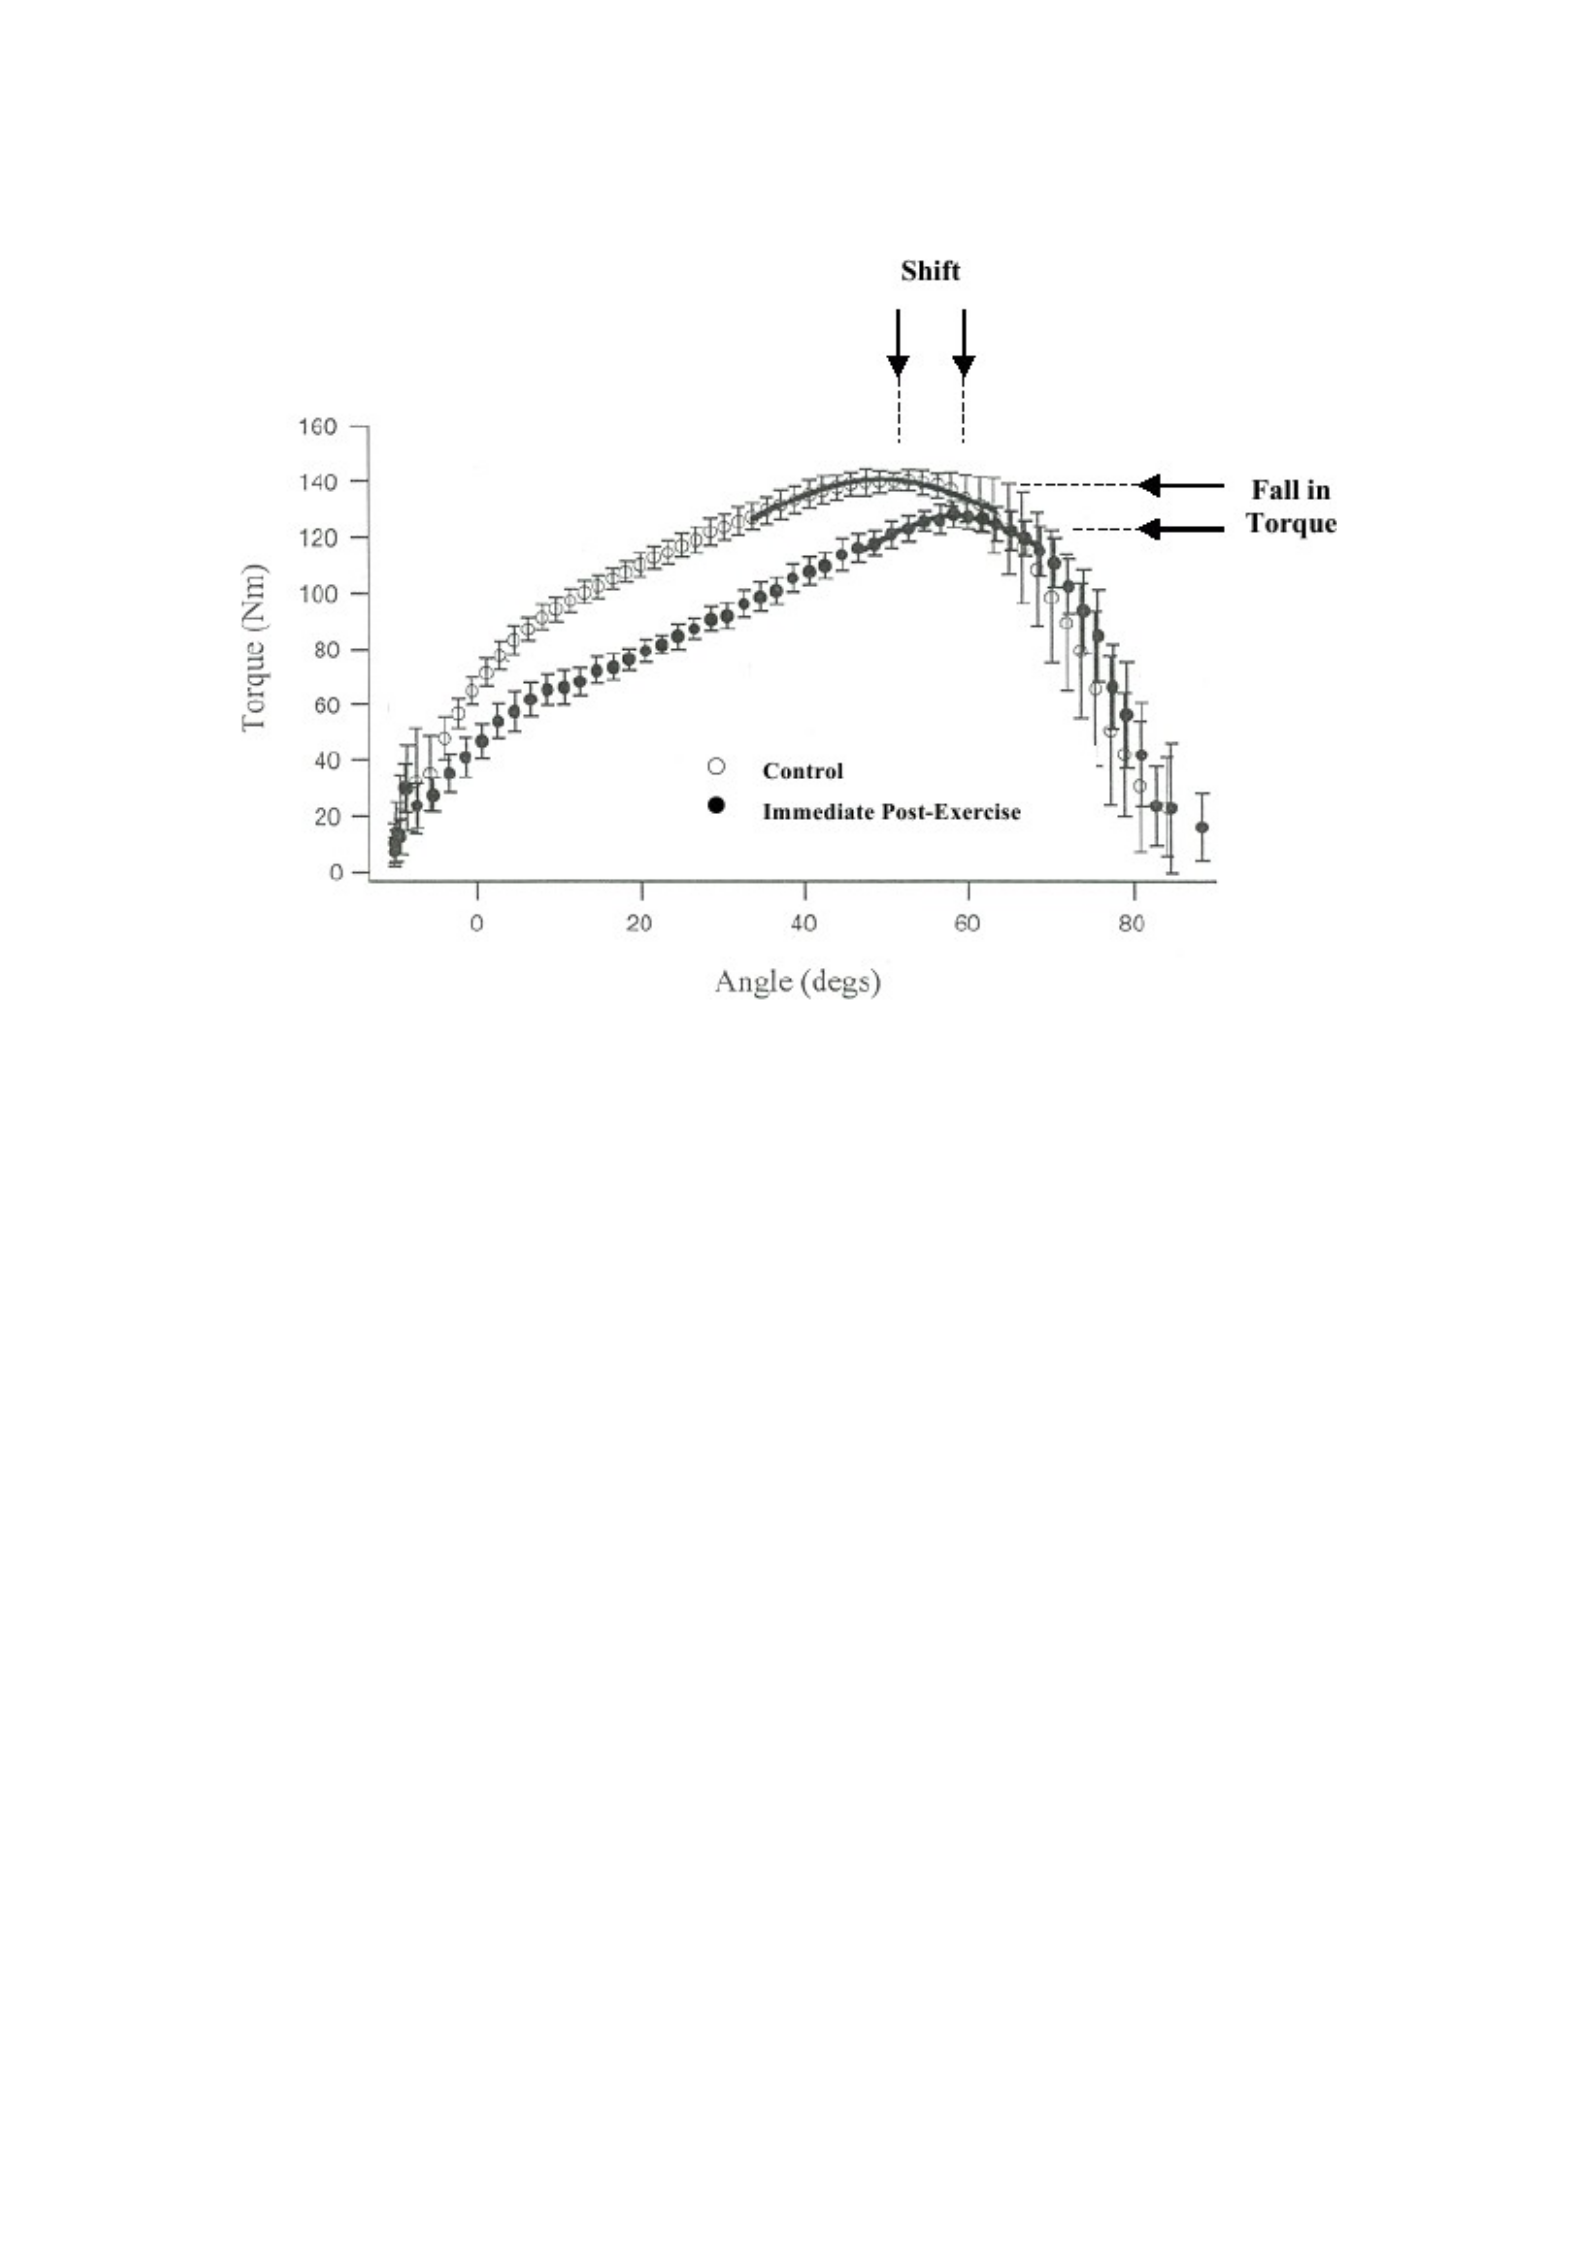
A shift in the length-tension relationship for a given force to longer muscle length
following eccentric exercise was first observed by Katz (1939), who proposed that rapid
over-stretching of muscle beyond its optimum length was likely to damage the contractile
elements. Katz’s original (1939) findings based on frog and tortoise muscle have been
confirmed by more recent investigations using human models (Jones et al., 1997;
Whitehead et al., 1998; Brockett et al., 2001; Philippou et al., 2003) (Figure 2.2).
These findings provide evidence to support the thesis that a longer muscle length is needed
to achieve the same myofilament overlap after eccentric exercise due to an increase in
series compliance resulting from the over-stretching of sarcomeres (Morgan & Allen, 1999;
Proske & Morgan, 2001). In further support of this theory, a greater loss in strength is
reported at short as opposed to longer or optimal muscle length following eccentric exercise
indicating a shift towards longer muscle lengths for maximal force generation (Saxton &
Donnelly, 1996; Child et al., 1998; Byrne et al., 2001; Sayers & Clarkson, 2001; Byrne &
Eston, 2002b).
28
Figure 2.2 Hamstrings angle-torque curves before eccentric exercise (Control) (O) and
immediately post exercise (●). Gaussian curves have been fitted to the top 10% of each
curve. Adapted from Brockett et al., (2001). Note the immediate right shift of the angle-
torque relationship following eccentric exercise.
2.4.2 Low-frequency fatigue
An alternative hypothesis to explain the loss in force-generating capacity and the shift in
the length-tension relationship proposes that alterations in calcium homeostasis may be
responsible. A decrease in the release of calcium ions (Ca2+) from the sarcoplasmic
reticulum (Warren et al., 1993; Westerblad et al., 1993) and an increase in intracellular Ca2+
(Chin & Allen, 1996) has been shown to lead to failure of the excitation-contraction (E-C)
coupling process in mouse muscle preparations. In human biopsy samples Hill et al. (2001)
have reported that sarcoplasmic reticulum Ca2+ release and uptake were significantly
depressed following exercise that provoked decrements in knee extensor MVC. These and

29
other authors have also observed a significant correlation between decreases in torque
production at low electrical stimulation frequencies and Ca2+ release following exercise
(Hill et al., 2001, Neilsen et al., 2005).
The disproportionate loss of force at low (20Hz) compared with high (100Hz) frequencies
of electrical stimulation is known as low-frequency fatigue (LFF) and is likely caused by an
impairment of excitation-contraction coupling process (Edwards et al,. 1977). It is known
to be induced by fatiguing exercise (Edwards et al., 1977; Newham et al., 1983b; Jones et
al., 1989), with the most profound effect provoked by eccentric exercise (Newham et al.,
1983b; Jones et al., 1989). Thus there is evidence from both animal and human studies to
suggest that reductions in sarcoplasmic reticulum Ca2+ release are the primary cause for
LFF. However, there is evidence that, in addition to reduced Ca2+ release, LFF that follows
eccentric exercise may be caused by changes in muscle morphology and subsequent
remodelling (Jones et al., 1996; Westerblad et al., 2000). The redistribution of sarcomere
lengths following eccentric exercise may account for the length-dependent effect of
strength loss associated with EIMD, particularly in view of the fact that, like decrements in
MVC, LFF is more evident at short rather than long muscle lengths. (Jones et al., 1989;
Byrne et al., 2001)
2.4.3 Alterations to neural control
The generation of muscular force is not only a product of muscle contractile function and
E-C coupling but also of neural drive. Therefore the inability to generate maximal force in
muscles damaged by eccentric exercise could theoretically be the result of alterations in
neural
drive,
estimates
of
which
can
be
obtained
using
electromyography
(EMG).

30
Deschenes et al. (2000) have provided evidence to suggest that neuromuscular efficiency,
the ratio of torque generated to integrated EMG (iEMG) activity, is decreased following
EIMD. These authors reported increases in iEMG activity and a decrease in the torque:
iEMG ratio during maximal isometric contractions which persisted for 10 days. Other
EIMD symptoms including plasma CK activity, perceived soreness and peak torque were
all recovered within 7 days (Deschenes et al., 2000). Subsequent investigations have
reported similar disturbances in the torque:iEMG ratio with the largest effect apparent at
low forces; arguably where the precision of force production is most functionally relevant
(Weerakkody et al., 2003a; Lavender & Nosaka, 2006; Semmler et al., 2007). Increased
isometric force fluctuations have also been observed following eccentric, muscle-damaging
exercise but they appear not to be an artefact of muscle damage as measures return to
baseline levels within 24 h (Lavender & Nosaka, 2006; Semmler et al., 2007).
Alterations have also been reported in the perception of force production and joint position
following eccentric exercise. Saxton et al. (1995) demonstrated that following eccentric
exercise of the forearm flexors, participants consistently overestimated the amount of force
they could produce. Rather than matching the target force of 35% MVC generated in the
undamaged (control) arm, participants undershot their target force for the 5 days of the
study following the initial insult (Saxton et al., 1995). However, when the forces applied
by both damaged and control arm were expressed as a proportion of the MVC for that arm
at that time, errors in estimation were reduced or absent (Saxton et al., 1995). In addition to
disturbances in the matching of a sense of force, disturbances in the reproduction of limb or
joint position have been reported following eccentric exercise (Saxton et al., 1995; Brockett
et al., 1997; Walsh et al., 2004). However, conflicting results were recorded. Brockett et

31
al. (1997) reported that participants produced larger joint angles following eccentric
exercise whereas Saxton et al. (1995) and Walsh et al. (2004) reported that participants
produced smaller joint angles following eccentric exercise. It has been proposed that
alterations to the perception of force and limb position following eccentric exercise may be
due to damaged sensory receptors within the muscle (Saxton et al., 1995; Brockett et al.,
1997; Carson et al., 2002; Proske et al., 2003). It is believed the sense of force is derived
from peripheral receptors in the muscle and the Golgi tendon organs and that muscle
spindles provide the signals for position sense (McCloskey, 1978; Gandevia, 1996). Twist
et al. (2008) reported impaired unilateral balance performance 24 h after plyometric,
muscle damaging exercise which the authors attributed to alterations in proprioceptive
control. However recent work by Gregory and colleagues using anaesthetised cat models
has demonstrated that the responsiveness of the tendon organs and muscle spindles is not
altered by eccentric exercise (Gregory et al., 2002, 2004). Thus the effect of eccentric,
muscle damaging exercise on proprioceptive function is yet to be explained.
It has been proposed that the increases in iEMG associated with altered proprioception
following EIMD may be indicative of altered motor unit activation (Proske et al., 2004;
Weerokkody et al., 2003b; Prasartwuth et al., 2005; Semmler et al., 2007). Proske et al.
(2003) have suggested that DOMS may be involved in alterations to neural control
following eccentric exercise. They propose that the pain from DOMS leads to a reduced
motor cortical excitability, which may serve to protect muscle during from further damage
during the repair process (Proske et al., 2003). However, the mechanism or mechanisms by
which EIMD influences alterations in motor unit recruitment remains to be determined.

32
2.5 The Repeated Bout Effect
The protective adaptation to a single bout of eccentric exercise has been termed the
‘repeated bout effect’ (Nosaka & Clarkson, 1995). Whenever unaccustomed eccentric
exercise is repeated, within a given time-frame, the magnitude of the characteristic
symptoms of EIMD is diminished. Changes in muscle morphology, muscle protein efflux,
inflammation, loss of strength and other symptoms are attenuated by a repetition of the
same exercise but the damaging effects are not prevented (Nosaka & Clarkson, 1995;
McHugh et al., 1999; McHugh, 2003). The repeated bout effect may be conferred as early
as 2 days after the initial exercise bout (Paddon-Jones et al., 2000; Nosaka & Newton,
2002) and for most of the symptoms of EIMD, lasts at least 6 months but is lost between 9
and 12 months (Nosaka et al., 2001a). Very little prior exercise is needed to confer the
effect. As few as 2 maximal eccentric contractions have been demonstrated to confer
protection against symptoms of EIMD when the same elbow flexor muscles performed 24
maximal contractions 2 weeks later (Nosaka et al., 2001b). Similarly Lavender and Nosaka
(2008) showed that light eccentric exercise, 30 (6 x 5) contractions of just 10% MVC was
effective in attenuating muscle damage against a subsequent bout of eccentric exercise of
40% MVC performed 48 h later.
The mechanisms underlying the repeated bout effect are not fully understood although
several potential mechanisms have been proposed. It has been suggested that protection is
conferred as a result of neural, cellular and mechanical adaptations which may work
independently of each other or in concert (McHugh et al., 1999; McHugh 2003). The
neural adaptation theory proposes that during a subsequent bout of eccentric exercise,
motor unit recruitment is altered in order to redistribute the workload and thus improve

33
motor unit efficiency (Nosaka & Clarkson, 1995). Warren et al. (2000) observed a 30%
decrease in EMG mean frequency in tibialis anterior muscle in the second of two bouts of
50 eccentric MVCs separated by one week. These authors concluded that the data
indicated that an increased activation of slow motor units and a concomitant decrease in
activation of fast units occurred in the repeated bout (Warren et al., 2000). The findings of
Chen (2003) lend further support to the thesis of reduced activation of fast-twitch motor
units during the second eccentric bout. However, McHugh et al. (2001) were unable to find
any evidence of neural adaptation after performing a repeated bout of relatively low-
intensity eccentric exercise.
The cellular adaptation theory involves potential adaptations of the contractile machinery.
Proske and Morgan (2001) have suggested that following eccentric exercise optimum
muscle length increases due to the addition of sarcomeres in series. A shift of optimum
angle towards a longer muscle length following EIMD has been confirmed in several
studies (see section 2.4.3). However, in a recent study, Chen and colleagues (2007a)
revealed that while a rightward shift in optimum angle demonstrated a relationship with the
degree of muscle damage associated with the initial bout, it did not appear to be directly
related to the mechanisms responsible for the repeated bout effect (Chen et al., 2007a).
Several investigations have used blood markers to show that there is a reduction in the
inflammatory response associated with EIMD following a repeated bout of eccentric
exercise (Pizza et al., 1996, 2001; Hirose et al., 2004; Smith et al., 2007). However, a more
recent study using muscle biopsy, demonstrated that several inflammatory genes were
transcriptionally up-regulated (rather than attenuated) following a repeated bout of
eccentric leg exercise (Hubal et al., 2008).

34
Mechanical adaptation to eccentric exercise may involve the remodelling of the
intermediate filament system to provide mechanical reinforcement against subsequent
bouts. Yu and Thornell (2002) showed that a single bout of downstairs running increased
staining of actin and desmin, suggesting that this reflected an increased synthesis of the
proteins as part of an adaptation process. More recently Lehti and colleagues (2007) have
used rat biopsy data to demonstrate that prior eccentric exercise produced an adaptive
response that protected the sarcolemma, intermediate filament, and sarcomeric proteins
against subsequent disruption. While there may be several mechanisms underlying the
repeated bout effect which may work in isolation or to compliment each other, a unified
theory to explain the mechanism of protective adaptation remains elusive.
The recently revealed presence of cross-over or contralateral adaptation to eccentric
exercise has indicated that the repeated bout effect is likely to involve a complex interplay
of all three proposed mechanisms (Howatson & van Someren, 2007). Following the second
bout of 45 eccentric MVCs of the elbow flexors, symptoms of EIMD were diminished
when the second bout was performed with the opposite or contralateral limb although the
magnitude of change was not as profound as when the same arm was exercised twice. The
authors have suggested that the contralateral adaptation was most likely mediated by neural
mechanisms as there was no direct stimulus for cellular of mechanical changes to the
contralateral arm (Howatson & van Someren, 2007). Thus the more profound adaptation to
the same-side arm most likely results from neural, cellular and mechanical mechanisms
working in concert.

35
2.6 Dynamic muscle function
Of all the symptoms of EIMD, the immediate and prolonged impairment to muscle function
has the potential to be the most debilitating when considering the human response to
dynamic exercise following eccentric exercise. However, the study of dynamic muscle
function during athletic performance has received only limited attention. The first study to
directly assess the influence of eccentric, muscle-damaging exercise on dynamic muscle
function was undertaken by Sargeant and Dolan (1987). These authors employed an
exhaustive downhill (-25%) walking intervention to induce damage followed by
assessments of maximal short term power output using an isokinetic cycle ergometer.
Cycling at 110 rev.min-1 for 20 s, peak power was reduced by 23% 24 h after the eccentric
exercise protocol and was still 8% lower than baseline values at 96 h (Sargeant & Dolan,
1987). Decrements in MVC were of a greater magnitude than peak power, with a loss of
45% of pre eccentric exercise values at 24 h, recovering to a 30% loss at 72h (Sargeant &
Dolan, 1987).
2.6.1 Wingate 30 s cycle test
These findings have been supported by Byrne and Eston (2002b) using a 30 s Wingate test
to investigate changes in power-generating ability following EIMD. These authors reported
decrements in peak power output and isometric MVC following the performance of 100
bar-bell squats with a load corresponding to 80% concentric one repetition maximum.
There were notable differences in both the magnitude of strength and power loss and their
recovery patterns. Isometric MVC dropped by 35% immediately after the squatting
protocol and then followed a linear recovery; 26% at 24 h and 19% at 48 h. In comparison,
Wingate peak power was reduced by 13% immediately after the eccentric intervention but

36
dropped further, by 18% at 24 h and 16% at 48 before recovery (Byrne & Eston, 2002b).
In a more recent study, Nottle and Nosaka (2007) employed a 40 min downhill (-7%)
running damage protocol to investigate changes in Wingate peak power. In agreement with
both Sargeant and Dolan (1987) and Byrne and Eston, 2002b), greater decrements were
observed in strength than peak power immediately after downhill running (17% and 5%,
strength and peak power, respectively), yet neither strength nor power loss persisted beyond
this initial post-eccentric exercise measurement. In contrast with the two previous studies
(Sargeant & Dolan, 1987; Byrne & Eston, 2002b), recovery was rapid and peak power was
unexpectedly 5% higher than baseline measures at 120 h (Nottle & Nosaka, 2007). An
earlier investigation, Malm et al. (1999) reported no change in Wingate peak power
following a stepping protocol designed to induce muscle damage. However, the modest
increase in soreness reported by participants and the unchanged CK response indicate that
the stepping protocol employed may not have been sufficiently intense to alter muscle
function.
2.6.2 Sprint performance
Malm and colleagues (1999) also reported the changes in the performance of intermittent
cycle sprint tests (10 x 10 s all-out cycling interspersed with 50 s rest periods) which
unexpectedly improved by 8% at 48 h. No change in 30 m running sprint performance was
observed 48 h after the completion of 70 (7 x 10) drop jumps designed to induce muscle
damage (Semark et al., 1999). However, participants in the study were well-trained rugby
union and field hockey players who, although they reported moderate soreness, showed no
elevation in plasma CK levels and may have been protected from alterations to muscle
function from the drop jumps via the repeated bout effect (see section 2.5). Effective

37
muscle-damaging protocols such as the 100 plyometric jumps employed by Highton et al.
(2009) have been shown to result in decrements in isokinetic peak torque and increases in 5
and 10 m sprint running times at 24 h and 48 h. Twist and Eston (2005) investigated the
influence of EIMD on both cycle and running sprint performance using 100 (10 x 10)
counter-movement jumps to induce damage. Peak power output during intermittent cycle
sprinting (10 x 6 s with 24 s recovery) was reduced immediately and up to 72 h after
eccentric exercise. The rate of fatigue in the cycle tests was also reduced with the greatest
decrease observed at 48 h. Similarly intermittent sprint running time (10 x 10 m with 12 s
active recovery) increased immediately and up to 48 h after eccentric exercise (Twist &
Eston, 2005). In a more recent investigation the same authors compared the performance of
a 10 s cycle sprint and a 50 cm drop jump at 24, 48 and 72 h after completing 100 (10 x 10)
counter-movement jumps (Twist & Eston, 2007). While performances of both the cycle
sprint and the drop jump were reduced as a result of the eccentric exercise the temporal
pattern of recovery was different. Peak power output and time to reach peak power were
most severely reduced at 48 h, whereas the greatest decrement in drop jump height was
observed at 24 h (Twist & Eston, 2007). This observation led the authors to propose that
differences in the response to cycling and drop jump performance indicate that the time
course of recovery from EIMD is dependent upon the mode of dynamic exercise (Twist &
Eston, 2007).
2.6.3 Vertical jump tests
Other studies have compared performance decrements in various vertical jumps in order to
investigate the effect of muscle-damaging exercise on dynamic muscle function. Byrne and
Eston (2002a) used 100 (10 x 10) barbell squats with a load of 70% body mass to identify

38
differences in the performance of squat jumps, counter-movement jumps and drop jumps
following eccentric, muscle-damaging exercise. The squat jump was performed from a
squatting position before jumping vertically for maximal height whereas in both the
counter-movement and drop jumps the muscle employed the stretch-shortening cycle
(SSC). The SSC of human muscle function is the natural mode of locomotion employed in
running, walking or jumping involving the cyclical performance of a sequence of pre-
activation, active (eccentric) braking followed by concentric action (Komi, 1984). The
reductions in vertical jump performance was immediate and lasted up to 72 h, although
squat jump performance was affected to a greater extent than either counter-movement or
drop jump performance. This observation prompted the authors to propose that impairment
of muscle function in the vertical jumps was attenuated when the SSC was used (Byrne &
Eston 2002a). Similar findings have been reported by Harrison and Gaffney (2004) who
used 70 (7 x 10) maximal eccentric contractions of the knee extensors to induce muscle
damage. In contrast, when muscle damage is induced via a SSC protocol (by means of a
specially designed sledge apparatus) rather than a predominantly eccentric protocol, drop
jump performance is more profoundly affected than squat jump performance (Avela et al.,
1999; Horita et al., 1999, 2003). These authors and others (e.g. Horita et al., 1996, Nicol et
al., 2006) have also reported a ‘bi-modal’ recovery from exhaustive SSC. The bi-modal
response involves an immediate post-exercise reduction in dynamic muscle function which
is believed to result primarily from metabolic fatigue. This is followed by a partial recovery
one to two hours post-exercise and a further reduction in dynamic muscle function which
has been attributed to the inflammatory response to EIMD (Nicol et al., 2006). However,
the phenomenon of a bimodal or biphasic response may not be exclusive to damage
induced via the SSC.
MacIntyre and colleagues (1996) were the first to report a biphasic

39
recovery of dynamic human muscle function following 300 repetitive eccentric contractions
of the knee extensors. Furthermore, few studies report measures of muscle function
between 0 and 24 h post exercise and those that do more frequently report static force than
dynamic torque (Clarkson & Hubal, 2002).
2.6.4 Endurance exercise
The immediate and prolonged loss of power-generating ability that results from muscle
damaging exercise also impedes performance during endurance exercise. Mice have been
used to investigate running time to exhaustion and the more ecologically valid, voluntary
wheel running time, following 150 min downhill running (Carmichael et al., 2005, 2006;
Davis et al., 2007). This group of authors has reported decreases in treadmill running time
to fatigue at 24, 48 and 72h. When compared to uphill running mice, one downhill group
ran 73% less at 24 h and 69% less at 48 h (Carmichael et al., 2005). Voluntary wheel
running activity was monitored during the 12 h active dark cycles following downhill
running in all three studies. The mice spent shorter time periods on the running wheel and
travelled reduced distances in the first and second 12 h active cycles, gradually returning to
baseline activity between day 3 (Carmichael et al., 2006; Davis et al., 2007) and day 5
(Carmichael et al., 2005).
To date, only two ecologically valid studies have investigated human endurance
performance following EIMD. Marcora and Bosio (2007) reported significant differences
in self-paced 30 min time trial running performance before and 48 h after the completion of
100 (10 x 10) drop jumps. Participants ran a shorter distance at a slower speed following
EIMD. An analysis of speed, heart rate and perceived exertion variables recorded during

40
the run indicated that pacing strategy was not altered. In light of these findings the authors
proposed that the negative effect of EIMD on time-trial performance was mediated by the
individuals’ perception of exertion (see section 2.8.2) (Marcora & Bosio, 2007). Twist and
Eston (2009) reported similar decrements in 5 min cycle time-trial performance following
100 (10 x 10) countermovement jumps. There were significant reductions in peak power
output (-14%), mean power output (-11%), mean revolutions per minute (RPM) (-4%), and
distance covered (-4%) 48 h after EIMD but performance measures had returned to baseline
at 168 h (Twist & Eston, 2009).
2.7 Human response to dynamic exercise
Investigations reporting changes in physiological parameters during exercise following
EIMD have produced equivocal findings. The first study to document physiological
changes during exercise with EIMD was undertaken by Hamill and colleagues (1991).
Steady-state oxygen uptake ( V˙ O2 ) and heart rate (HR) data were recorded during a 15
min
run at 80% maximal V˙ O2 ( V˙ O 2 max ) before and after a 30 min bout of downhill running (at
a gradient of -15%). The V˙ O2
and HR responses of the ten recreational runners were
unchanged at 48 and 120 h after downhill running. The small, albeit significant increase in
CK activity and the development of only moderate soreness led the authors to suggest that
the downhill run may have provided insufficient stress to elicit metabolic or HR
modifications (Hamill et al., 1991). These authors also reported small but significant
decreases in hip and knee flexion during running following EIMD but overall performance
of the stride, including stride length, stride period, mechanical work, and mechanical power
was unaffected (Hamill et al., 1991).

41
2.7.1 Oxygen uptake
Measures of V˙ O2 during running at a fixed sub-maximal speed, such as those procured by
Hamill and colleagues (1991), provide information relating to the cost or economy of
locomotion, more commonly termed ‘running economy’. In contrast to Hamill et al.’s
(1991)findings, Braun and Dutto (2003) reported that running economy was significantly
compromised (average 3.2% increase in V˙ O2 ) during 5 min running bouts at 65, 75 and
85% V˙ O2 peak, 48 h after a 30 min downhill run (-10%) at an intensity equivalent to 70%
V˙ O2
peak.
Furthermore, these authors reported decreases in the mean stride length at all
three exercise intensities which were negatively correlated to changes in the mean energy
cost of running at all three exercise intensities (Braun & Dutto, 2003). A comparison of the
training status of the two participant groups (Hamill et al., 1991; Braun & Dutto, 2003) was
suggested as an important factor in explaining the disparate findings (Braun & Dutto,
2003). The well-trained runners in the Braun and Dutto (2003) study may have had more
refined gait patterns than the recreational runners in the Hamill et al. (1991) study. Thus
the trained runners may have been more sensitive to changes in gait resulting from muscle
damage. In support of this suggestion, Paschalis et al. (2005) reported no change in the
economy data of untrained athletes during running at approximately 55 and 75% V˙ O2 max
during the 3 days following completion of 120 (12 x 10) eccentric MVCs. Similarly,
Marcora and Bosio (2007) reported no change in the running economy of active, but not
highly trained distance runners, exercising at 70%
V˙ O 2 max for 10 min 48 h after the
completion of 100 (10 x10) drops jumps. Another study using active but not highly trained
participants also reported unaltered running economy following a series of sub-maximal
resistance exercises including barbell squat, weighted lunges and weighted step-ups (Scott

42
et al., 2003). It was suggested by these authors that the extent of muscle damage induced
was insufficient to produce mechanical or physiological changes that would influence V˙
O2
(Scott et al., 2003). Chen and colleagues (2007b) have provided the only evidence of the
time course of changes in running economy following EIMD. Running economy data were
collected for five consecutive days following the completion of a 30 min downhill run (-
15%) at an intensity equivalent to 70% V˙ O2 peak (Chen et al., 2007b).
Using the same
submaximal exercise intensities as Braun and Dutto (2003) (65, 75 and 85% V˙ O2 peak)
these authors demonstrated that running economy was compromised by 4-7% for three days
after the downhill running, recovering to near baseline levels on day four (Chen et al.,
2007b). In addition, reductions in stride length (3-6%), range of motion (ROM) of the
ankle and knee joints (1-7%) and increases in stride frequency (3-7 %) were observed for
two to three days following the downhill running. These authors concluded that the time
course and magnitude of alterations in economy were more closely related to changes in
kinematic parameters than changes in muscle function as indicated by immediate and
prolonged changes in MVC (reduction of 7-21% for 4 days after downhill running) (Chen
et al., 2007b).
Measures of economy have also been assessed during cycling at a fixed sub-maximal load
and are not as susceptible to the effects of alterations in lower limb kinematics as it has
been suggested that running economy is. In fact there is consistent evidence that EIMD
does not alter cycling economy irrespective of the mode of damage employed or the
training status of the participants (Gleeson et al., 1995; Walsh et al., 2001; Moysi et al.,
2005; Schneider et al., 2007; Twist & Eston, 2009). Gleeson et al. (1995) and Schneider et

43
al. (2007) employed untrained participants who were required to perform bench-stepping

44
protocols to induce muscle damage. Participants in the other three studies were all
physically active but not highly trained and were required to perform eccentric cycling
(Walsh et al., 2001), barbell squatting (Moysi et al., 2005) and countermovement jumps
(Twist & Eston, 2009) in order to induce muscle damage. No change in V˙ O2
measures
was reported in any of the aforementioned studies during sub-maximal constant load
cycling. Furthermore, it has been reported that peak V˙ O2 measured during incremental
cycling to exhaustion was unaffected by a prior bout of eccentric, bench-stepping exercise
(Gleeson et al., 1998). The observation that cycling is not susceptible to the potentially
confounding influence of altered kinematics makes it a particularly attractive model with
which to examine the effect of EIMD on the human response to dynamic exercise. The
fixed geometry of a cycle ergometer ensures that hip and knee angles remain relatively
constant during exhaustive cycling exercise despite the development of significant localised
muscle fatigue (Dingwell et al., 2008). In contrast, reductions of up to 7% in the range of
motion of the knee joint have been reported during running following the downhill running.
(Chen et al., 2007b).
2.7.2 Oxygen uptake kinetics and muscle oxygenation
While measurements of V˙ O2 at constant sub-maximal speeds or loads provide information
relating to the energy cost of locomotion, the rate at which O2 uptake increases at exercise
onset ( V˙ O2 kinetics) can provide information pertaining to the balance of O2 delivery to
O2 utilisation in active skeletal muscle.
Schneider and colleagues (2007) were the first to
investigate the influence of EIMD on O2 uptake kinetics. Nine untrained participants each
performed square-wave transitions from unloaded to heavy intensity cycling before and 48

45
and 72 hours after completing 30 min of bench-stepping exercise. The heavy intensity
exercise was determined as the work load equivalent to 40% of the difference (40 %∆)
between the power output achieved at the gas exchange threshold (GET) and that achieved
at peak V˙ O2 . The phase II V˙ O2
kinetics were unaltered by the prior eccentric exercise
indicating that EIMD did not compromise oxidative function or alter the matching of O2
delivery to O2utilisation in the active muscle tissue. In addition, the unchanged slow
component indicated that the O2 cost of cycling at 40 %∆ was not altered. These findings
led the authors to speculate that they had not induced sufficiently severe muscle damage to
elicit changes in
V˙ O2
kinetics. While muscle oxygenation was not measured in this
investigation, near-infrared spectroscopy (NIRS) can facilitate the assessment of muscle
oxygenation and can therefore be used to non-invasively determine the dynamic balance
between O2
delivery and O2
utilisation.
Walsh et al. (2001) examined the kinetics of
O2
utilisation and re-oxygenation during
ischemia and reperfusion at rest before and 2 days after 30 min of eccentric cycling.
No
change was reported in O2
utilisation or local O2
transport with the authors concluding
that muscle oxidative function at rest was not impaired as a result of EIMD (Walsh et al.,
2001). More recently Ahmadi et al. (2008) used NIRS to investigate O2
saturation and
desaturation kinetics at rest and during isometric contractions at 30, 50 and 80% MVC
before and after a 40 min bout of downhill walking (-25%). In contrast to the findings of
Walsh and colleagues (2001), Ahmadi et al. (2008) reported immediate and prolonged
speeding
of
the
NIRS-derived O2 kinetics.
The
authors
proposed
that
the
probable
mechanism for the increased O2 saturation and desaturation may have been increased O2

46
utilisation due to the requirements of energy demanding repair processes (Ahmadi et al.,
2008). However the authors did concede that increases in muscle blood flow subsequent to
EIMD, such as reported by Laaksonen et al. (2006), may have been responsible for the
apparent speeding of O2 saturation and desaturation kinetics (Ahmadi et al., 2008). While
muscle oxygenation kinetics have been investigated at rest and during isometric
contractions, to date, no study has attempted to investigate the influence of EIMD on
muscle oxygenation kinetics during the performance of dynamic exercise.
2.7.3 Metabolic responses to dynamic exercise
As detailed in section 2.6.4, the reduction in resting muscle glycogen uptake following
EIMD has led to speculation that increased glygogenolysis may be a consequence of EIMD
and as such may be responsible for increases in blood lactate concentration ([La]) observed
at rest (Asp et al., 1996, Asp et al., 1998) and during dynamic exercise (Braun & Dutto,
2003; Chen at al., 2007b, 2008; Gleeson et al., 1995, 1998).
Gleeson et al. (1995) were the first to report increases in immediate post exercise [La] 48 h
after a 30 min bout of bench-stepping designed to induce muscle damage. Participants
cycled for 15 min at an intensity equivalent to 80% V˙ O 2 max
48 h after either the eccentric
bench-stepping exercise or concentric uphill walking. Pre-exercise [La] was not different
between the two groups but it was higher after eccentric exercise (7.5 mmol.l-1) than after
concentric exercise (6.0 mmol.l-1). In a follow-up study, blood samples were taken before
and at 2 min intervals throughout an incremental cycle test to exhaustion and demonstrated
that following eccentric exercise [La] increased (Gleeson et al., 1998). In this investigation
the control condition was unexercised in the period prior to completion of the incremental

47
exercise test and demonstrated lower [La] during and 2 min after completion of the test
(Gleeson et al., 1998). These authors proposed that the higher blood [La] in the post
eccentric condition reflected a higher intramuscular [La] and an increased relative
contribution of anaerobic metabolism to energy production possibly arising from additional
recruitment of type II muscle fibres (Gleeson et al., 1998). In support of this suggestion
Braun and Dutto (2003) have reported increased blood [La] during running at 65, 75 and 85
% of peak V˙ O2 . Blood samples were taken during the 5 min rest period after each 5 min
bout and were on average 0.61 mmol.l-1 higher 48 h after the downhill running protocol.
The increase in [La], attributed to a greater reliance on glycolytic energy production,
together with altered stride mechanics were suggested as contributory factors in the
reduction in running economy (Braun & Dutto, 2003) (previously discussed in section
2.7.3). Similarly, Chen et al. (2007b) reported significant increases in [La] in blood
samples taken 3 min after the completion of each 5 min running bout at 65, 75 and 85%
V˙ O2 peak.
The authors suggested that the increases in [La] which lasted for three
days
following a 30 min downhill run may have reflected increased motor unit activation (Chen
et al., 2007b).
However, elevations in [La] may not reflect alterations in metabolic function following
EIMD.
Schneider et al. (2007) reported unchanged phase II V˙ O2 kinetics indicating that
EIMD did not compromise oxidative function (see section 2.7.3) together with elevations in
[La]. The difference between resting and end exercise blood [La] was higher following
EIMD and was attributed to an increased lactate efflux from the active muscle due to
increased membrane permeability rather than to an enhanced rate of anaerobic glycolysis

48
(Schneider et al., 2007). An increased lactate efflux may be countered by increased muscle

49
blood flow following EIMD (Laaksonen et al., 2006) which could facilitate greater [La]
clearance by improving transport to lactate metabolising muscle and other tissues.
Increased muscle blood flow may well explain for the unchanged blood [La] reported in
other studies (Hamill et al., 1991; Scott et al., 2003; Marcora & Bosio, 2007) and the
reduced blood [La] reported by Moysi et al. (2005) following EIMD.
Magnetic resonance spectroscopy (MRS) can be used to measure parameters of muscle
metabolic function including the dynamic changes in the ratio of inorganic phosphate to
phosphocreatine (Pi/PCr) and intracellular pH. Several studies have shown a significant
decrease in the resting PCr/Pi ratio following EIMD, which could be interpreted as an
increase in metabolism following the muscle injury (McCully et al., 1992; Lund et al.,
1998a, 1998b). However, due to fact that no commercially available ergometers are
capable of functioning within a MRS, only one study has investigated possible alterations
to muscle metabolism following EIMD during dynamic leg exercise inside the core of a
whole body MRS. Using a hydraulic ergometer specifically designed for quadriceps
exercise within a whole body MRS (Rodenburg et al., 1994), participants completed two
graded concentric exercise tests before and 24 h after performing stepping exercise
designed to induce EIMD (Rodenburg et al., 1995). The expected decrease in the resting
PCr/Pi ratio was observed but no differences were reported in the PCr/Pi ratio during the
exercise test. While these findings indicated that exercise metabolism was not altered by
the stepping exercise, the lack of change in several markers of muscle damage including
plasma CK activity, led the authors to conclude that muscle metabolism could feasibly be
altered by more severe EIMD (Rodenburg et al., 1995). The inconclusive nature of this one
set of findings suggests that further research employing MRS should be conducted in order

50
to more clearly illustrate the effect of EIMD on muscle metabolism during dynamic
exercise.
2.7.4 Ventilatory responses to dynamic exercise
The mechanisms which control ventilation during dynamic exercise are controversial but
are believed to involve elements of proportional feedback (central and carotid
chemosensory) and feed-forward (central command and muscle reflex) in varying
proportions (Ward, 2007). Below the lactate threshold, ventilation is involved in the
regulation of the arterial partial pressure of CO2 to near baseline levels. Above the lactate
threshold bicarbonate buffering of the lactic acidosis provides an important stimulus to
ventilation.
Several investigations have reported no change in ventilation following EIMD. Paschalis et
al. (2005) employed the lowest intensity exercise, with participants running at “randomly
selected velocities” of 133 and 200 m.min-1 which were equivalent to ~ 55 and ~75%
V˙ O 2 max respectively (Paschalis et al., 2005). When compared to baseline measures, no
change in ventilation was reported at either velocity for 4 days after completion of 120 (12
x 10) eccentric MVCs. Similarly, Scott et al. (2003) and Marcora and Bosio (2007) have
reported an unaltered ventilatory response to running at intensities equivalent to a blood
[La] of 2.5 mmol.l-1 (ostensibly below the lactate threshold) and 70% V˙ O ,
2 max
respectively.
Furthermore, these authors observed no influence of EIMD on blood [La]
(Scott et al., 2003; Marcora & Bosio, 2007).
Participants in the study conducted by Moysi
et al. (2005) cycled at 62% V˙ O 2 max for 6 min before and 48 h after completing a series of
muscle damaging squats. While no overall change in minute ventilation was reported the

51
authors did observe increases in breathing frequency which were countered by decreases in
tidal volume. An explanation for these observations and for the observation that blood [La]
was decreased by 12% at 48 was not offered (Moysi et al., 2005).
Increases in ventilation in conjunction with increases in blood [La] have been reported
during running at 65, 75 and 85% V˙ O 2 max
following EIMD (Braun & Dutto, 2003; Chen et
al. 2007b, 2008) and have been associated with impaired running economy attributed to
altered lower limb kinematics (see section 2.7.1). However, Gleeson et al. (1995) observed
increases in both ventilation and blood [La] during cycling at 80% ˙
2
max
48 h after
eccentric exercise. Minute ventilation was increased from 6-15 min of a 15 min bout and
was mainly due to a higher breathing frequency. Similarly, Schneider et al. (2007) reported
increases in both ventilation and blood [La] during cycling at 40%∆ (heavy intensity
exercise). While the influence of the increased lactic acidosis was considered the most
likely explanation, the increased stimulation of muscle nociceptors due to increased muscle
pain and the higher perception of effort reported were also proposed as potential
mechanisms to drive the increase in ventilation (Gleeson et al., 1995; Schneider et al.,
2007).
Schneider et al. (2007) have provided the only example of an investigation using a specific
exercise domain to study the influence of EIMD on physiological responses to dynamic
exercise. The exercise domain employed during an investigation is important in
determining the individual physiological response to dynamic exercise. Markedly different
metabolic, cardiorespiratory and perceived exertion responses are elicited from the three
sub-maximal exercise intensity domains (moderate, heavy and severe). As such, it is

52
important that exercise intensity is accurately defined by delineating the boundaries
between these domains when investigating these responses (Jones et al., 2009). The vast
majority of studies investigating the influence of EIMD on the performance of dynamic
exercise utilise exercise intensities determined by a percentage of maximal work capacity.
This can be rather misleading due to inter-individual differences. For example, exercise at
80% V˙ O 2
max
(e.g. Gleeson et al., 1995), may result in one individual exercising within the
heavy domain whilst another exercises within the severe domain. Future research
involving the influence of EIMD on ventilatory and other human responses to dynamic
exercise should endeavour to use specific exercise domains so that the interpretation of
findings is not confounded by individuals exercising at different relative intensities.
Increases in ventilation following EIMD may be linked to an increased lactic acidosis,
however other potential mechanisms have been investigated. In order to eliminate the
influence of metabolic control factors such as [La], Hotta and colleagues (2006)
investigated the ventilatory response to the first 20 s of dynamic knee extension exercise
following EIMD. Knee extensions with ankle weights of approximately 2.5% body mass
were repeated five to seven times. The breath by breath data were time aligned to the start
of exercise, ensemble averaged and then linearly interpolated to yield 1 s data points.
Ventilation at the onset of exercise was significantly elevated 2 and 7 days after eccentric
exercise leading the authors to suggest that alterations in the peripheral neural reflexes
contributed to the enhanced ventilatory response (Hotta et al., 2006).

53
2.7.5 Perception of effort during dynamic exercise
The perception of effort involves the assimilation of a number of afferent signals from
various perceptual cues emanating from different body systems including the
cardiorespiratory and neuromuscular systems which can be interpreted in both a feedback
and feed-forward manner (Hampson et al., 2001). Cues may be peripheral, produced for
example by the painful stimulation of muscle afferents following EIMD; or centrally-
derived from the cardiorespiratory responses to exercise. While the damage protocol, the
exercise mode and the exercise intensity may have a significant influence on many other
physiological responses, the weight of evidence suggests that EIMD results in an increased
sense of effort during dynamic exercise (Gleeson et al., 1995; Scott et al., 2003; Marcora &
Bosio, 2007; Chen et al., 2007b, 2008; Twist &Eston, 2009).
Gleeson et al. (1995) reported an increased sense of effort during cycling at 80% V˙ O 2 max
2
days after completing 30 min of bench-stepping. The higher ratings of perceived exertion
(RPE) reported were believed to reflect the weakened state of the muscles, the increase in
blood [La] and the sensation of muscle soreness (Gleeson et al., 1995). Increases in RPE
have also been reported during running following eccentric exercise (Scott et al., 2003;
Chen et al. 2007b, 2008). Scott and colleagues (2003) suggested that perceived exertion
was the best indicator of physical stress as RPE is a configuration of responses resulting
from an integration of signals, perceptions and experiences. In addition to the cues
proposed by Gleeson and colleagues (1995), altered neural control was suggested as a
possible cue to the higher perception of exertion reported following EIMD (Scott et al.,
2003). Recent studies conducted by Marcora and Bosio (2007) and Twist and Eston (2009)
have reported RPE responses during fixed-load submaximal exercise and time trial

54
performance. During running for 10 min at 70% V˙ O 2
max
(Marcora & Bosio, 2007) and
cycling for 5 min at 60 and then 80% of maximal power output (Twist & Eston, 2009) RPE
was higher following eccentric exercise. However, during both the running and cycling
time trials RPE was unchanged following EIMD although time trial performances were
significantly reduced. Both pairs of investigators concluded that following EIMD an
altered sense of effort mediated performance. Participants reported higher RPEs when
exercising at the same intensity and produced less force (slower running or cycling speed)
when perceiving the same effort (Marcora & Bosio, 2007; Twist and Eston, 2009).
Several studies have demonstrated alterations in the perception of force production
following eccentric exercise which persist for several days (see section 2.4.3). More recent
investigations have corroborated these findings, proposing that participants were using their
perception of the effort required to generate a given torque rather than the level of torque
itself (Carson et al., 2002; Proske et al., 2003; Weerakkody et al., 2003a; Proske et al.,
2004). These findings indicate that EIMD impairs the perception of effort or exertion rather
than the ability to match a given force as participants with EIMD with EIMD produce
reduced force for a given perceived effort and perceive higher effort when producing the
same force.
2.8 Conclusion
Direct histological analyses of muscle tissue and indirect measures of the structural and
functional status of skeletal muscle following unaccustomed, eccentric exercise are well
documented and have revealed substantial disruption. However, the effects of exercise-
induced muscle damage on the human response to dynamic exercise have been investigated

55
infrequently and have produced equivocal findings. Exercise modality has been found to
influence the human response following EIMD with changes observed during running more
closely related to changes in kinematic parameters than changes in muscle function.
Therefore cycling, which is not susceptible to the potentially confounding influence of
altered kinematics, is the preferred model with which to examine the effect of EIMD on the
human response to dynamic exercise. The purpose of the following studies is to investigate
the influence of EIMD on various human responses during the performance of dynamic
exercise. Specifically, investigations will focus on ventilatory and perceived exertion
responses, muscle metabolism, muscle oxygenation kinetics and pulmonary oxygen uptake.

56
CHAPTER 3:
COMMON METHODS

57
3.1 Introduction
The experiments which comprise this thesis were conducted in the exercise physiology
laboratories of the School of Sport and Health Sciences at the University of Exeter which
are accredited by the British Association of Sport and Exercise Science. In Study 3
(chapter 6) 31P-magnetic resonance spectroscopy was conducted at the Peninsula Magnetic
Resonance Research Centre at the University of Exeter. Prior to the collection of any data
all participants gave written informed consent to participate in the research, which was
approved by the School of Sport and Health Sciences Ethics Committee.
3.2 Familiarisation
Most of the participants recruited were members of the School of Sport and Health
Sciences at the University of Exeter and were familiar with the experimental testing
protocols and associated procedures. However as maximal and/or exhaustive effort was
required on most visits to the laboratory, appropriate practice was conducted. Participants
in all four studies were fully familiarised with the production of maximal voluntary
contractions using a Biodex B-2000 isokinetic dynamometer (Biodex Corp, Shirley, NY).
All participants in study 3 (chapter 6) were required to complete a familiarisation session in
a ‘mock MRI system’. During this session, participants practised single-legged, knee-
extension exercise at a rate of 40 repetitions/min in time with a visual cue projected onto
the front wall of the ‘mock’ scanner room. Vigorous encouragement was given to
participants throughout all maximal and/or exhaustive tests to ensure a maximal effort was
produced.

58
3.3 Eccentric muscle-damaging exercise protocol
In order to provoke muscle damage, participants in each of the four studies were required to
perform 100 squats as 10 sets of 10 repetitions using a Smith machine (Figure 3.1).
Figure 3.1 A participant being guided in the correct and safe squatting technique prior
to completion of 100 (Smith) squats.
This procedure involved the controlled, isotonic resistance of the external load of the bar,
which was calculated to correspond to approximately 70% of each participant’s body mass.
This was calculated to within 5 kg of the predicted 70% body mass as the smallest available
weights were 2.5 kg.
Prior to commencement, participants were instructed in correct and

59
safe lifting technique (see appendix E for risk analysis). Before the bar was disengaged it
was positioned on the participant’s shoulders and feet were positioned under the bar.
During the movement the participant’s head was kept forward, the back straight and legs
fully extended (knee = 180°). Feet were kept flat on the floor, toes pointing forward, with
equal distribution of weight through fore-foot and heel. Prior to commencement, the
appropriate foot position was marked on the floor with tape so that it could be reproduced
in each of the ten sets of ten repetitions. The descent phase involved eccentric action of the
knee extensors to lower the bar to a knee angle of just past 90°. The lifting phase involved
concentric action to return the bar to the starting position. In order to facilitate the
consistent production of 90° squats, a plastic metre rule was taped to the safety stop frame
on the guide rod using gaffer tape to provide a visual and audible guide for the participant
and investigators. When the participant achieved the required angle this could be seen in
the facing mirror and heard as the metre rule contacted the base frame of the Smith
machine.
During pilot work, a metronome was used in an attempt to control the speed of contraction
as it has been suggested that this may influence the magnitude of damage induced
(Chapman et al., 2006). However, participants struggled to maintain a set cadence of four
down to one up with the metronome set at 60 beats per minute without losing form.
Therefore this element of the protocol was abandoned and participants were encouraged to
perform controlled decent and lifting phases at their own pace whilst maintaining the
correct and safe lifting technique. After each set of ten repetitions a minimum rest period of
1 minute was allowed with participants encouraged to take as much time as they needed
between sets to ensure that the correct and safe lifting technique could be maintained.

60
3.4 Markers of muscle damage
In a review of measurement tools used to evaluate exercise-induced muscle damage,
Warren et al. (1999) proposed that maximal voluntary contraction (MVC) torque provided
the best measure of muscle damage resulting from eccentric contractions. These authors
were dismissive of using either changes in perceived muscle soreness or changes in the
blood levels of myofibre proteins such as Creatine Kinase (CK) as they are reported to
correlate poorly with the magnitude and time course of changes in muscle function (Warren
et al., 1999). However, we chose to include measures of soreness and plasma CK activity
in addition to those of MVC torque, in order to provide a wider physiological perspective
of the damage induced. In each study these markers of muscle damage were assessed in the
order listed below before and after completing the eccentric, muscle-damaging exercise in
order to measure the effectiveness of the protocol.
3.4.1 Creatine Kinase activity
Plasma CK activity was assessed from fingertip capillary samples. The sample was
centrifuged at 4000 RPM (2000 x g) for 5 minutes and two 20 µl samples of plasma were
then added to 1 ml of a composition of reagents supplied by Randox (CK-NAC 110,
Randox Laboratories Ltd., Crumlin, Co. Antrim, UK). Following 1 min incubation at 37˚C
and during continued incubation, absorbance at 340 nm was recorded by spectrophotometry
(Jenway 6310 spectrophotometer, Jenway, Essex, UK) at 0, 1, 2 and 3min. CK values were
calculated using the formula CK(U/l) = 8095 x Δ absorbance 340 nm/min. The mean CK
value of the two samples was calculated and used for subsequent analysis. Normal serum
values of 24-195 U/l are reported for men using this method (Szasz et al., 1976). The intra-

61
assay coefficient of variation for duplicate samples using this procedure in our laboratory
was 6.6 %.
3.4.2 Perceived muscle soreness
Participants assessed the soreness of their knee extensors using a blank 0–10 visual
analogue scale (VAS) (Appendix G). The VAS consisted of a 10 cm line labelled from left
(no soreness) to right (worst soreness ever). After squatting to approximately 90o knee
flexion with hands on hips, participants were asked to place a mark on the VAS to indicate
their level of soreness. Perceived pain was then quantified by measuring the distance to the
mark on the line to the nearest 0.1 cm. This procedure has been used in previous studies
(Rowlands et al., 2001; Twist and Eston, 2005, 2007).
3.4.3 Isokinetic peak torque
Following familiarisation sessions, isokinetic peak torque of the knee extensors was
measured using a Biodex B-2000 isokinetic dynamometer (Biodex Corp, Shirley, NY),
which was calibrated prior to each data collection session in accordance with the
manufacturer’s guidelines (Figure 3.2).
62
Figure 3.2 The assessment of isokinetic peak torque, using a Biodex B-2000 isokinetic
dynamometer (Biodex Corp, Shirley, NY)
The initialisation, system diagnostics and calibration procedures were performed
automatically by the Biodex System by pressing the Start key on the control panel.
Participants completed a standardised warm-up of 2 minutes cycling at 50 W on an
electronically braked cycle ergometer (Lode Excalibur Sport, Groningen, Netherlands)
followed
by
static
stretching
exercises
of
the
knee
extensor/flexor
muscle
groups.
Participants completed a standardised warm-up of 2 minutes cycling at 50 W on the cycle
ergometer followed
by static stretching exercises of the knee extensor/flexor muscle
groups. The participants were then seated in the isokinetic dynamometer in an upright
position with the seat angle set at 85°. The ankle was secured to the input arm of the
dynamometer on the tibia allowing full ankle motion, with the rotational axis of the
dynamometer aligned
with
the
lateral
femoral
epicondyle. All adjustments
to
the

63
dynamometer were recorded and replicated in subsequent tests.
The 80° range of motion

64
for each subject (from 90º to 10º knee flexion (full extension = 0°)) was manually
established by the investigator and confirmed goniometrically. The mass of the limb was
recorded by the dynamometer to enable the gravitational correction of peak torque values.
The highest of five maximal voluntary contractions (MVCs) at an angular velocity of 30
deg.s-1 was recorded. A 30-s rest period was allowed between contractions. Visual
feedback, displaying real time force and strong verbal encouragement were used to promote
maximal effort. All data were collected using the Biodex Advantage Software package and
stored on the computer for subsequent analysis. The inter-test coefficient of variation for
duplicate measures using this procedure in our laboratory was 4.9 %.

The contents of this chapter form the basis of the following publication:
Davies RC, Rowlands AV, Eston RG. Effect of exercise-induced muscle damage on
ventilatory and perceived exertion responses to moderate and severe intensity cycle
exercise. European Journal of Applied Physiology 2009; 107 (1):11-9.
65
CHAPTER 4:
THE EFFECT OF EXERCISE-INDUCED MUSCLE DAMAGE ON
VENTILATORY AND PERCEIVED EXERTION RESPONSES TO MODERATE
AND SEVERE INTENSITY CYCLE EXERCISE

66
4.1 Abstract
This study examined the effect of exercise-induced muscle damage (EIMD) on ventilatory
and perceived exertion responses to cycle exercise. Ten healthy, physically active men
cycled for six minutes at moderate intensity and to exhaustion at severe intensity before and
48 h after eccentric exercise (100 squats with a load corresponding to 70% of body mass).
Changes in ventilation and ratings of perceived exertion (RPE) were calculated for each
individual and expressed against time (moderate and severe exercise) and as a percentage
of time to exhaustion (severe exercise).
Ventilation increased during moderate exercise at
48 h ( V˙
E
; 34.5 ± 5.0 to 36.3 ± 3.8 L.min-1, P<0.05) but increases in RPE were not
significant.
During severe exercise at 48 h, time to exhaustion (TTE) was reduced and V˙ E
(87.1 ± 14.1 to 93.8 ± 11.7 L.min-1) and RPE (15.5 ± 1.3 to 16.1 ± 1.4) were elevated
(P<0.05). When expressed as a percentage of TTE, the differences in ventilation and RPE
values disappeared. Findings indicate that the augmented ventilatory response to cycle
exercise following EIMD may be an important cue in informing effort perception during
high intensity exercise but not during moderate intensity exercise.

67
4.2 Introduction
Unaccustomed exercise, particularly exercise with a high eccentric component, has a
significant impact on muscle structure and function. However, the influence of EIMD on
submaximal exercise performance remains equivocal. During submaximal running, reports
of elevated oxygen consumption ( V˙ O2 ), minute ventilation ( V˙
E
), respiratory
exchange ratio (RER), blood lactate concentration ([La]) and heart rate (HR) (Braun &
Dutto, 2003; Chen et al., 2007b, 2008) are countered by observations of unaltered
cardiorespiratory and metabolic responses (Hamill et al., 1991; Scott et al., 2003; Paschalis
et al., 2005; Marcora & Bosio, 2007).
During submaximal cycling, the V˙ O2 response does not appear to be altered by a prior
bout of eccentric, muscle-damaging exercise (Gleeson et al., 1995; Moysi et al., 2005;
Schneider et al., 2007; Twist & Eston, 2009). However the influence of EIMD on other
cardiorespiratory and metabolic responses remains in dispute. Elevated V˙
E
and HR
responses have been reported during high intensity cycling 48 h after damage-inducing,
bench-stepping and have been associated with increases in [La] (Gleeson et al., 1995;
Schneider et al., 2007). During lower intensity exercise (62% V˙ O2 max ) following squatting
exercise, V˙
E
, HR and [La] appear to be unchanged (Moysi et al., 2005).
Thus it would
appear that mode of damage induction and the intensity and mode of exercise are important
factors in determining the response to submaximal exercise with EIMD. However,
irrespective of the mode of damage, exercise intensity, or exercise protocol employed, the
weight of evidence supports the premise that eccentric, muscle-damaging exercise results in

68
an increased sense of effort (Gleeson et al., 1995; Scott et al., 2003; Marcora & Bosio,
2007; Chen et al., 2007b, 2008; Twist & Eston, 2009).
Impaired force-generation consequential to EIMD results from reduced neural input to the
muscle which serves as a protective mechanism to prevent further injury (Proske et al.,
2004). Similarly, the higher ratings of perceived exertion (RPEs) reported during sub-
maximal exercise following EIMD may also contribute to a putative centrally-mediated
protective system. The perception of effort involves the assimilation of numerous afferent
signals from a range of perceptual cues emanating from various body systems including the
cardiorespiratory and neuromuscular systems, which can be interpreted in both a feedback
and feed-forward manner (Hampson et al., 2001).
The cues which inform the perceptual response to exercise may arise from central or
peripheral sensations. Central cues, which reflect the aerobic demands of the exercise
(Åstrand & Ryhming, 1954), are derived from the cardiorespiratory system, whereas
peripheral cues include local muscle sensations (such as painful muscles) and sensations
produced by the stimulation of mechanoreceptors and chemoreceptors (Watt & Grove,
1993; Robertson & Noble, 1997). The influence of central (cardiorespiratory) cues is less
important than that of local sensations, particularly at lower exercise intensities (Mihevic,
1981; Hampson et al., 2001). Thus, the perception of exertion reported during exercise
with EIMD may be differentially influenced by central and peripheral cues dependent on
the exercise intensity.

69
The exercise domain employed during investigations is important in determining the
cardiorespiratory and perceived exertion responses. The three sub-maximal exercise
intensity domains (moderate, heavy and severe) elicit markedly different metabolic,
physiological and perceived exertion responses. The physiological events which separate
the different exercise domains are the lactate threshold, which marks the transition from the
moderate to heavy intensity exercise and the maximum lactate steady-state or critical
power, which marks the transition from heavy to severe intensity exercise. Thus, it is
important that exercise intensity is accurately defined by delineating the boundaries
between these domains when investigating such responses (Jones et al., 2009).
Investigations that utilise exercise intensity as determined by a percentage of maximal work
capacity can be misleading due to inter-individual differences.
For example, exercise at
80% V˙ O2 max ,
an
intensity
typically
used
to
investigate
the
influence
of
EIMD
on
submaximal exercise performance (e.g. Gleeson et al., 1995; Twist & Eston, 2009), may
result in one individual exercising within the heavy domain while another may be within
the severe domain.
Therefore, the purpose of this study was to investigate changes in ventilatory and perceived
exertion responses to cycling with and without exercise-induced muscle damage.
Specifically, to investigate these changes during 6 minutes of moderate intensity cycle
exercise and exhaustive, severe intensity cycle exercise. We hypothesised that eccentric
muscle-damaging exercise would elevate the ventilatory response to severe intensity
exercise but would not alter the response during moderate intensity exercise. In addition,
we predicted that following prior eccentric exercise the perceived exertion responses to

70
cycle exercise at both exercise intensities would be elevated and that the scalar time
property of perceived exertion during exercise to exhaustion would not be affected.
4.3 Method
Participants
Ten healthy, physically active men volunteered to participate in the study. All were
asymptomatic of illness and pre-existing injuries and had not participated in any resistance
training of the lower limbs for at least six months prior to assessment. Their characteristics
are shown in Table 4.1. Participants gave written informed consent to participate in the
research, which was approved by the Ethics Committee of the School of Sport and Health
Sciences at the University of Exeter (See appendices B, C and D for exemplar participant
information sheet, participant consent form and ethical approval certificate).
Table 4.1 Participant characteristics (N = 10).
Characteristic Mean (± SD)
Age (yrs) 21.5 (± 1.2)
Height (m) 1.82 (± 0.06)
Mass (kg) 79.8 (± 8.2)
Max V˙ O2 (ml kg min )
. -1 -1 48 (± 3)
Max HR (beats.min-1) 194 (± 6)
Max WR (W) 353 (± 30)
WR at GET (W) 120 (± 14)
Moderate WR (W) 96 (± 11)
Severe WR (W) 283 (± 24)
Maximal (max), gas exchange threshold (GET) and other work rate (WR) values are those measured during
the ramp test.

71
Participants were requested not to take any anti-inflammatory drugs for the duration of the
study and were instructed to report to the laboratory in a rested state, having completed no
strenuous exercise in the preceding 24 h. Changes in V˙ O2 kinetics and
deoxyhaemoglobin
kinetics due to EIMD were assessed in a sub-sample and this data has been reported
elsewhere (Chapter 7).
Procedures
Exercise testing
Participants were required to visit the laboratory at the same time of day (± 1 h) on four
occasions over a 3-week period. All testing was performed on an electronically braked
cycle ergometer (Lode Excalibur Sport, Groningen, Netherlands). During the first visit,
after measurement of height and body mass (SECA, Hamburg, Germany) participants
completed an incremental (ramp) cycle exercise test to exhaustion to establish maximal
oxygen uptake ( V˙ O2 max ) and gas-exchange threshold (GET) and to establish future work
intensities (Table 4.1). Participants cycled at a self-selected pedal rate (between 70 and 90
rpm) and this pedal rate along with the saddle and handlebar height and configuration were
recorded and reproduced in subsequent tests. The ramp test consisted of 4 minutes of
baseline cycling at 0 W followed by a continuous increase in work rate of 1 W every 2 s
(i.e. 30 W.min−1) until the subject was unable to continue.
The V˙ O was identified as
2 max
the highest 30-s mean value recorded prior to the participant’s volitional termination of the
test. The GET was determined independently by two experienced reviewers using the V-
slope method (Beaver et al., 1986).
This involves visual inspection of individual plots of

72
V˙ CO2
against V˙ O2
to establish the first disproportionate increase in V˙ CO2 . The work
rates that required 80% of the GET (moderate exercise) and 70% of the difference ()

73
between the GET and V˙ O2
max
(severe exercise) were calculated, with account taken of the
mean response time of the V˙ O2 adaptation to ramp exercise (approximately 2/3 of the
ramp rate i.e. minus 20 W) (Whipp et al., 1981). On the second and fourth visits, before and
48 h after eccentric exercise, respectively, participants cycled at a self-selected pedal rate
(between 70 and 90 rpm) for six min at a constant work rate (WR) of 80% GET (moderate).
After six min rest, participants cycled at a constant work rate of 70% (severe intensity)
and continued until volitional termination of the test at exhaustion. Participants received
strong verbal encouragement to continue exercising for as long as possible in all exhaustive
tests.
Eccentric exercise
On the third visit participants completed the eccentric, muscle-damaging exercise protocol
which comprised 100 (Smith) squats performed as 10 sets of 10 repetitions. The load on the
bar was calculated to correspond to 70% of each participant’s body mass. For further
details of these procedures please refer to Chapter 3.
Measurements
Markers of muscle damage
Markers of muscle damage (muscle soreness and isokinetic peak torque) were measured
immediately before and then 30 minutes and 48 hours after eccentric exercise. In addition
plasma creatine kinase (CK) activity was assessed immediately before and then 30 minutes,
24 and 48 hours after eccentric exercise. Due to availability at 24 h, only 8 participants
were measured for CK activity.

74
Perceived soreness of the knee extensors was assessed using a blank 0–10 visual analogue
scale (VAS). The VAS consisted of a 10 cm line labelled from left (no soreness) to right
(worst soreness ever). Participants squatted to 90o knee flexion with hands on hips and then
placed a mark on the VAS to indicate their level of soreness. Perceived pain was then
quantified by measuring the distance from 0 to the mark on the line to the nearest 0.1 cm.
Plasma CK activity was assessed from fingertip capillary samples. The sample was
centrifuged at 4000 RPM (2000 x g) for 5 minutes and two 20 µl samples of plasma were
then added to 1 ml of reagents (Randox CK-NAC 110, Randox Laboratories Ltd., Crumlin,
Co. Antrim, UK). The solution was then incubated at 37˚C and absorbance at 340 nm was
recorded by spectrophotometry (Jenway 6310 spectrophotometer, Jenway, Essex, UK) at 1,
2 3 and 4 min. CK values were calculated using the formula CK(U/l) = 8095 x Δ
absorbance 340 nm/min. The mean CK value of the two samples was calculated and used
for subsequent analysis. Normal serum values of 24-195 U/l are reported for men using this
method (Szasz, 1976). The intra-assay coefficient of variation for duplicate samples using
this procedure in our laboratory was 6.6 %.
Isokinetic peak torque was measured using a Biodex B-2000 isokinetic dynamometer
(Biodex Corp, Shirley, NY), which was calibrated prior to each data collection session in
accordance with the manufacturer’s guidelines. Following familiarization sessions,
participants performed five maximal voluntary contractions (MVCs) at 30 deg·s-1 with a
rest period of 30 s between contractions. The inter-test coefficient of variation for duplicate
measures using this procedure in our laboratory was 4.9 %.
Visual feedback, displaying

75
real time force, was used to encourage maximal effort. For further details of these
procedures please refer to Chapter 3.
Exercise test measures
Pulmonary gas exchange was measured breath-by-breath via an online gas analysis system
(Cortex MetaMax 3B, Biophysik, Leipzig, Germany) throughout all exercise tests. Changes
in breathing frequency (fR), minute ventilation ( V˙
E
), oxygen uptake ( V˙ O2 ) and V˙
E
/ V˙
O2
were recorded continuously during the tests via the Cortex Metasoft 3.1 software. The
system was calibrated prior to every test in accordance with manufacturer’s guidelines
against known concentrations of cylinder gases (15% oxygen, 5% carbon dioxide) and a 3-l
calibration syringe (for flow volume). Heart rate (HR) was monitored using a wireless
chest strap telemetry system (Polar Electro T31, Kempele, Finland) and recorded
continuously via a link to the Cortex gas analysis system in all exercise tests.
Participants were familiarised with Borg’s 6-20 Rating of Perceived Exertion (RPE) Scale
and provided with standardised instructions on how to employ the scale (Borg, 1998).
Participants were encouraged to focus on their overall perception of exertion when
reporting their RPE, which were recorded during the last 15 seconds of each minute of all
exercise tests (Figure 4.1).
The blood lactate response was assessed from fingertip blood samples collected
immediately before and immediately after the moderate and severe intensity exercise bouts.
Samples were collected into a Lithium heparin microvette (CB300, Sarstedt AG & Co.,

76
Nümbrecht, Germany) and were subsequently analysed for blood lactate concentration
using a YSI 2300 STAT plus analyzer (Yellow Springs, Ohio, USA).
Figure 4.1
RPE Scale. A participant reporting his RPE during cycle exercise using the Borg 6-20
Statistical analysis
Markers of muscle damage
Changes in the markers of muscle damage (isokinetic peak torque, perceived muscle
soreness and creatine kinase activity) were analysed using a series of one way repeated
measures analyses of variance (ANOVAs).
Data were initially checked for assumptions of
normality and as the CK activity data were not normally distributed; these values were log-

77
transformed prior to statistical analysis. Following transformation CK activity data were
normally distributed (see appendix H).
Exercise test measures
Changes in fR,V˙
E
,
V˙ O2 , HR, V˙
E
/ V˙ O2 and RPE were calculated for each individual and
expressed against time (minute values) for both moderate and severe intensity exercise, and
in the case of severe exercise, as a % of time to exhaustion (% time). These values were
analysed via a series of two-factor (test x time) fully repeated measures ANOVAs. Where
assumptions of sphericity were violated (P <.05) the Greenhouse-Geisser (GG) correction
factor was applied to adjust the degrees of freedom. Where a significant test x time
interaction was observed, post hoc Tukey tests modified for repeated measures (Stevens,
2002) were run to determine where significant differences occurred. Paired t-tests were
used to determine significant differences in blood lactate concentration [La] and time to
exhaustion during severe intensity exercise pre- and post-eccentric exercise. All data were
analysed using the statistical software package SPSS for Windows (version 13). Statistical
significance was set at 0.05. A P-value of between 0.05 and 0.10 was considered a trend.
4.4 Results
Markers of muscle damage
The eccentric exercise was effective in provoking significant changes in all markers of
muscle damage. Table 4.2 shows changes in isokinetic peak torque, muscle soreness and
CK activity before and after eccentric exercise. Isokinetic peak torque (30 deg.s-1)
decreased to 86% of pre damage values at 30 min recovering to 89% at 48h (F (2, 18) = 13.37

78
P < 0.001). Significant soreness was reported 30 min after eccentric exercise with the

79
highest values reported at 48 h (F (2, 18) = 71.49 P < 0.001). CK activity increased after
eccentric exercise, with the highest values observed at 24 h (FGG (1.4, 9.8) = 13.13 P < 0.05).
Table 4.2 Changes in markers of muscle damage. Mean (± SD) values before (pre) and
30min and 48h after eccentric exercise
Measured variable pre 30 min 24 h 48 h
CK activity (U/l) 178 ±129 244 ± 181 794 ± 690* 88 ± 217
Soreness 0.5 (0.5) 5.4 (1.6)* n/a 6.8 (1.6)*
Peak Torque (Nm) 30 deg.s-1 279(45) 239 (28)* n/a 248 (35)*
N = 10, Soreness and Peak Torque; N = 8, CK activity* Significantly different from pre value (P < 0.05).
Exercise test measures
Moderate intensity exercise
Table 4.3 shows mean (± SD) changes fR, V˙E , V˙ O2 , HR, V˙E / V˙ O2 and RPE respectively
during cycling at moderate intensity (80% GET) pre and 48 h post eccentric exercise. Main
effects for test for fR (F (1, 9) = 7.29, P = 0.024), V˙
E
(F (1, 9) = 6.36, P = 0.033) and HR (F
(1,
9) = 12.52, P = 0.006) indicated an increase in values following eccentric exercise.
There
were no significant differences in V˙ O2 , V˙E / V˙ O2 or RPE as a result of eccentric exercise
(P > 0.05). Similarly, there were no significant differences in pre and post exercise blood
lactate concentration before and after eccentric exercise (pre: 1.13 ± 0.43, 1.08 ± 0.29 and
post: 0.98 ± 0.21, 1.10 ± 0.28 mmol.l-1 before and after eccentric exercise, respectively) (P
> 0.05).

80
Table 4.3 Changes in fR, V˙E , V˙ O2 ,HR, V˙E / V˙ O2 and RPE during moderate
intensity exercise. Mean (± SD) values before (pre) and 48h after (post) eccentric exercise.
fR
V˙ E
V˙
O2
HR V˙E /
V˙ O2
RPE
(breaths.min-1) (L.min-1) (ml.kg-1.min-1) (Beats.min-1)
Pre 20.6 (± 3.5) 34.5 (± 5.0) 19.9 (± 0.9) 109 (± 7) 21.8 (± 1.6) 9.9 (± 1.7)
Post 21.8 (± 3.2)* 36.3 (± 3.8)* 20.1 (± 1.8) 116 (± 8)* 22.7 (± 1.2) 10.6 (± 1.6)
* Significantly different from pre value (P < 0.05) N = 10
Severe intensity exercise to exhaustion
As expected, time to exhaustion was significantly reduced following eccentric exercise
(7.33 ± 2.26, 6.37 ± 2.16 min pre- and post-eccentric exercise, respectively) (t (9) 2.64, P =
0.027). Before eccentric exercise all 10 participants completed a minimum of 5 min severe
intensity. However, 48 h after eccentric exercise the minimum time achieved by all
participants was reduced to 4 min. Pre-exercise [La] was unchanged, but end-exercise [La]
was significantly lower following eccentric exercise (t (9) = 3.31, P =0.009) (pre-exercise:
0.90 ± 0.34, 0.79 ± 0.34 and end exercise: 9.33 ± 1.73, 8.45 ± 1.51 mmol.l-1 before and
after eccentric exercise, respectively).
Minute-by-minute measures
In order to investigate minute-by-minute changes in fR, V˙E , V˙ O2 ,HR, V˙E / V˙ O2 and RPE,
the first 4 minutes of data were analysed. Figure 4.2 a–f shows minute-by-minute changes
for minutes 1-4 in fR, V˙
E
, V˙ O2 , HR, V˙
E
/ V˙ O2
and RPE respectively during cycling at
70%∆ pre and post eccentric exercise. A main effect for time was observed for all

81
variables (P < 0.05).
Main effects for test for fR (F (1, 9) = 10.53, P = 0.010), V˙
E
(F (1, 9) =
9.50, P = 0.013), V˙E / V˙ O2 (F (1, 9) = 8.47, P = 0.017), and RPE (F (1, 9) = 8.15, P = 0.019)
and a trend for HR (F (1, 9) = 4.43, P = 0.065) showed that values had increased following
eccentric exercise. There was an interaction (test*time) for fR (FGG (1.3, 11.3) = 5.25, P =
0.036) and V˙E (F (3, 27) = 3.19, P = .039). Post hoc tests indicated that following eccentric
exercise, fR and V˙E were significantly higher for all but the first minute of exercise. There
were no significant differences in V˙ O2 (P > 0.05).
Percentage time values
Figure 4.3 a–f shows % time changes in fR, V˙E , V˙ O2 , HR, V˙E / V˙ O2 and RPE respectively
during cycling at 70%∆ pre and post eccentric exercise. When expressed as a % of time to
volitional exhaustion, the main effects for time remained but the main effects for test for fR,
V˙E , HR and RPE disappeared. However, there was a main effect for test for V˙ O2 (F (1,
9) = 5.25, P = 0.048) which showed that values had decreased following eccentric
exercise. This was accompanied by an increase in V˙E / V˙ O2 (main effect, F (1, 9) = 5.17,
P = 0.049).
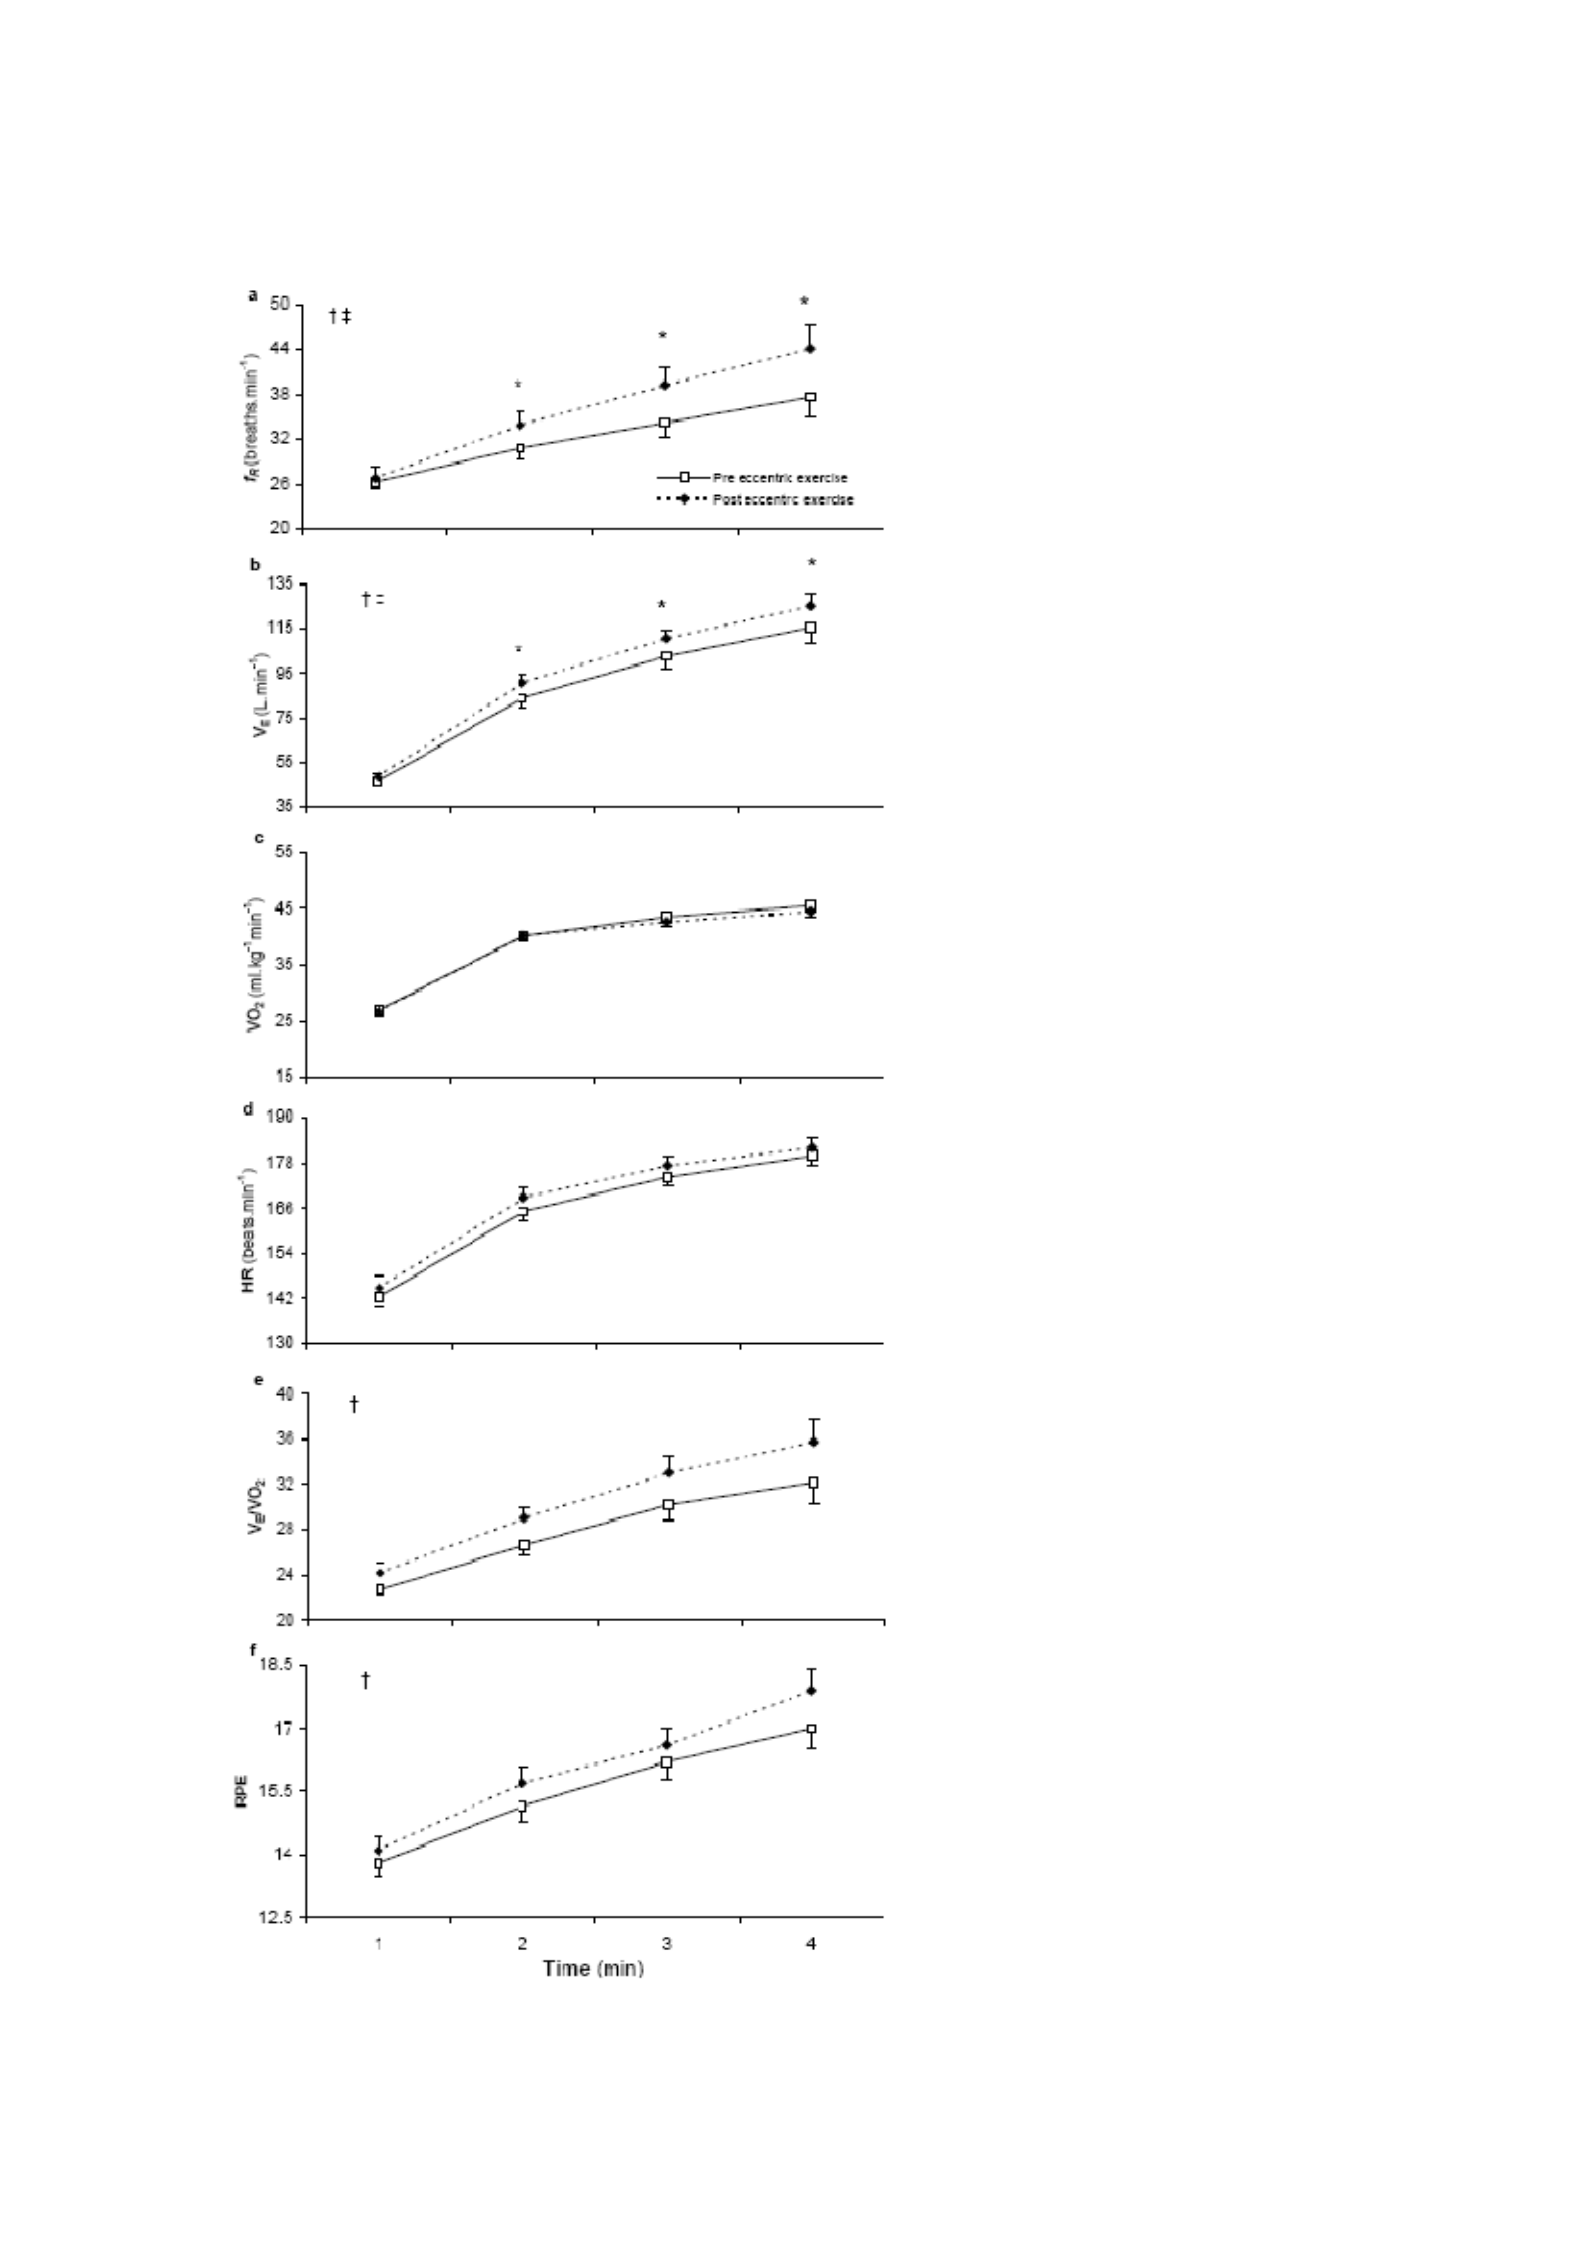
82
Figure 4.2
Minute values (severe intensity
exercise). Minute-by-minute
changes in a: breathing frequency
(fR), b: minute ventilation ( V˙
E
),
c: oxygen uptake ( V˙ O2 ), d:
HR, e: V˙E / V˙ O2 and f: RPE
during cycling at 70%∆ pre- and
48h post- eccentric exercise.
Values are mean (± SEM).
Significant main effect for time for
all measures (P < 0.05).
† Significant main effect for test (P
< 0.05).
‡ Significant interaction effect
(test*time) (P < 0.05).
* Significantly different from pre
value (P < 0.05).
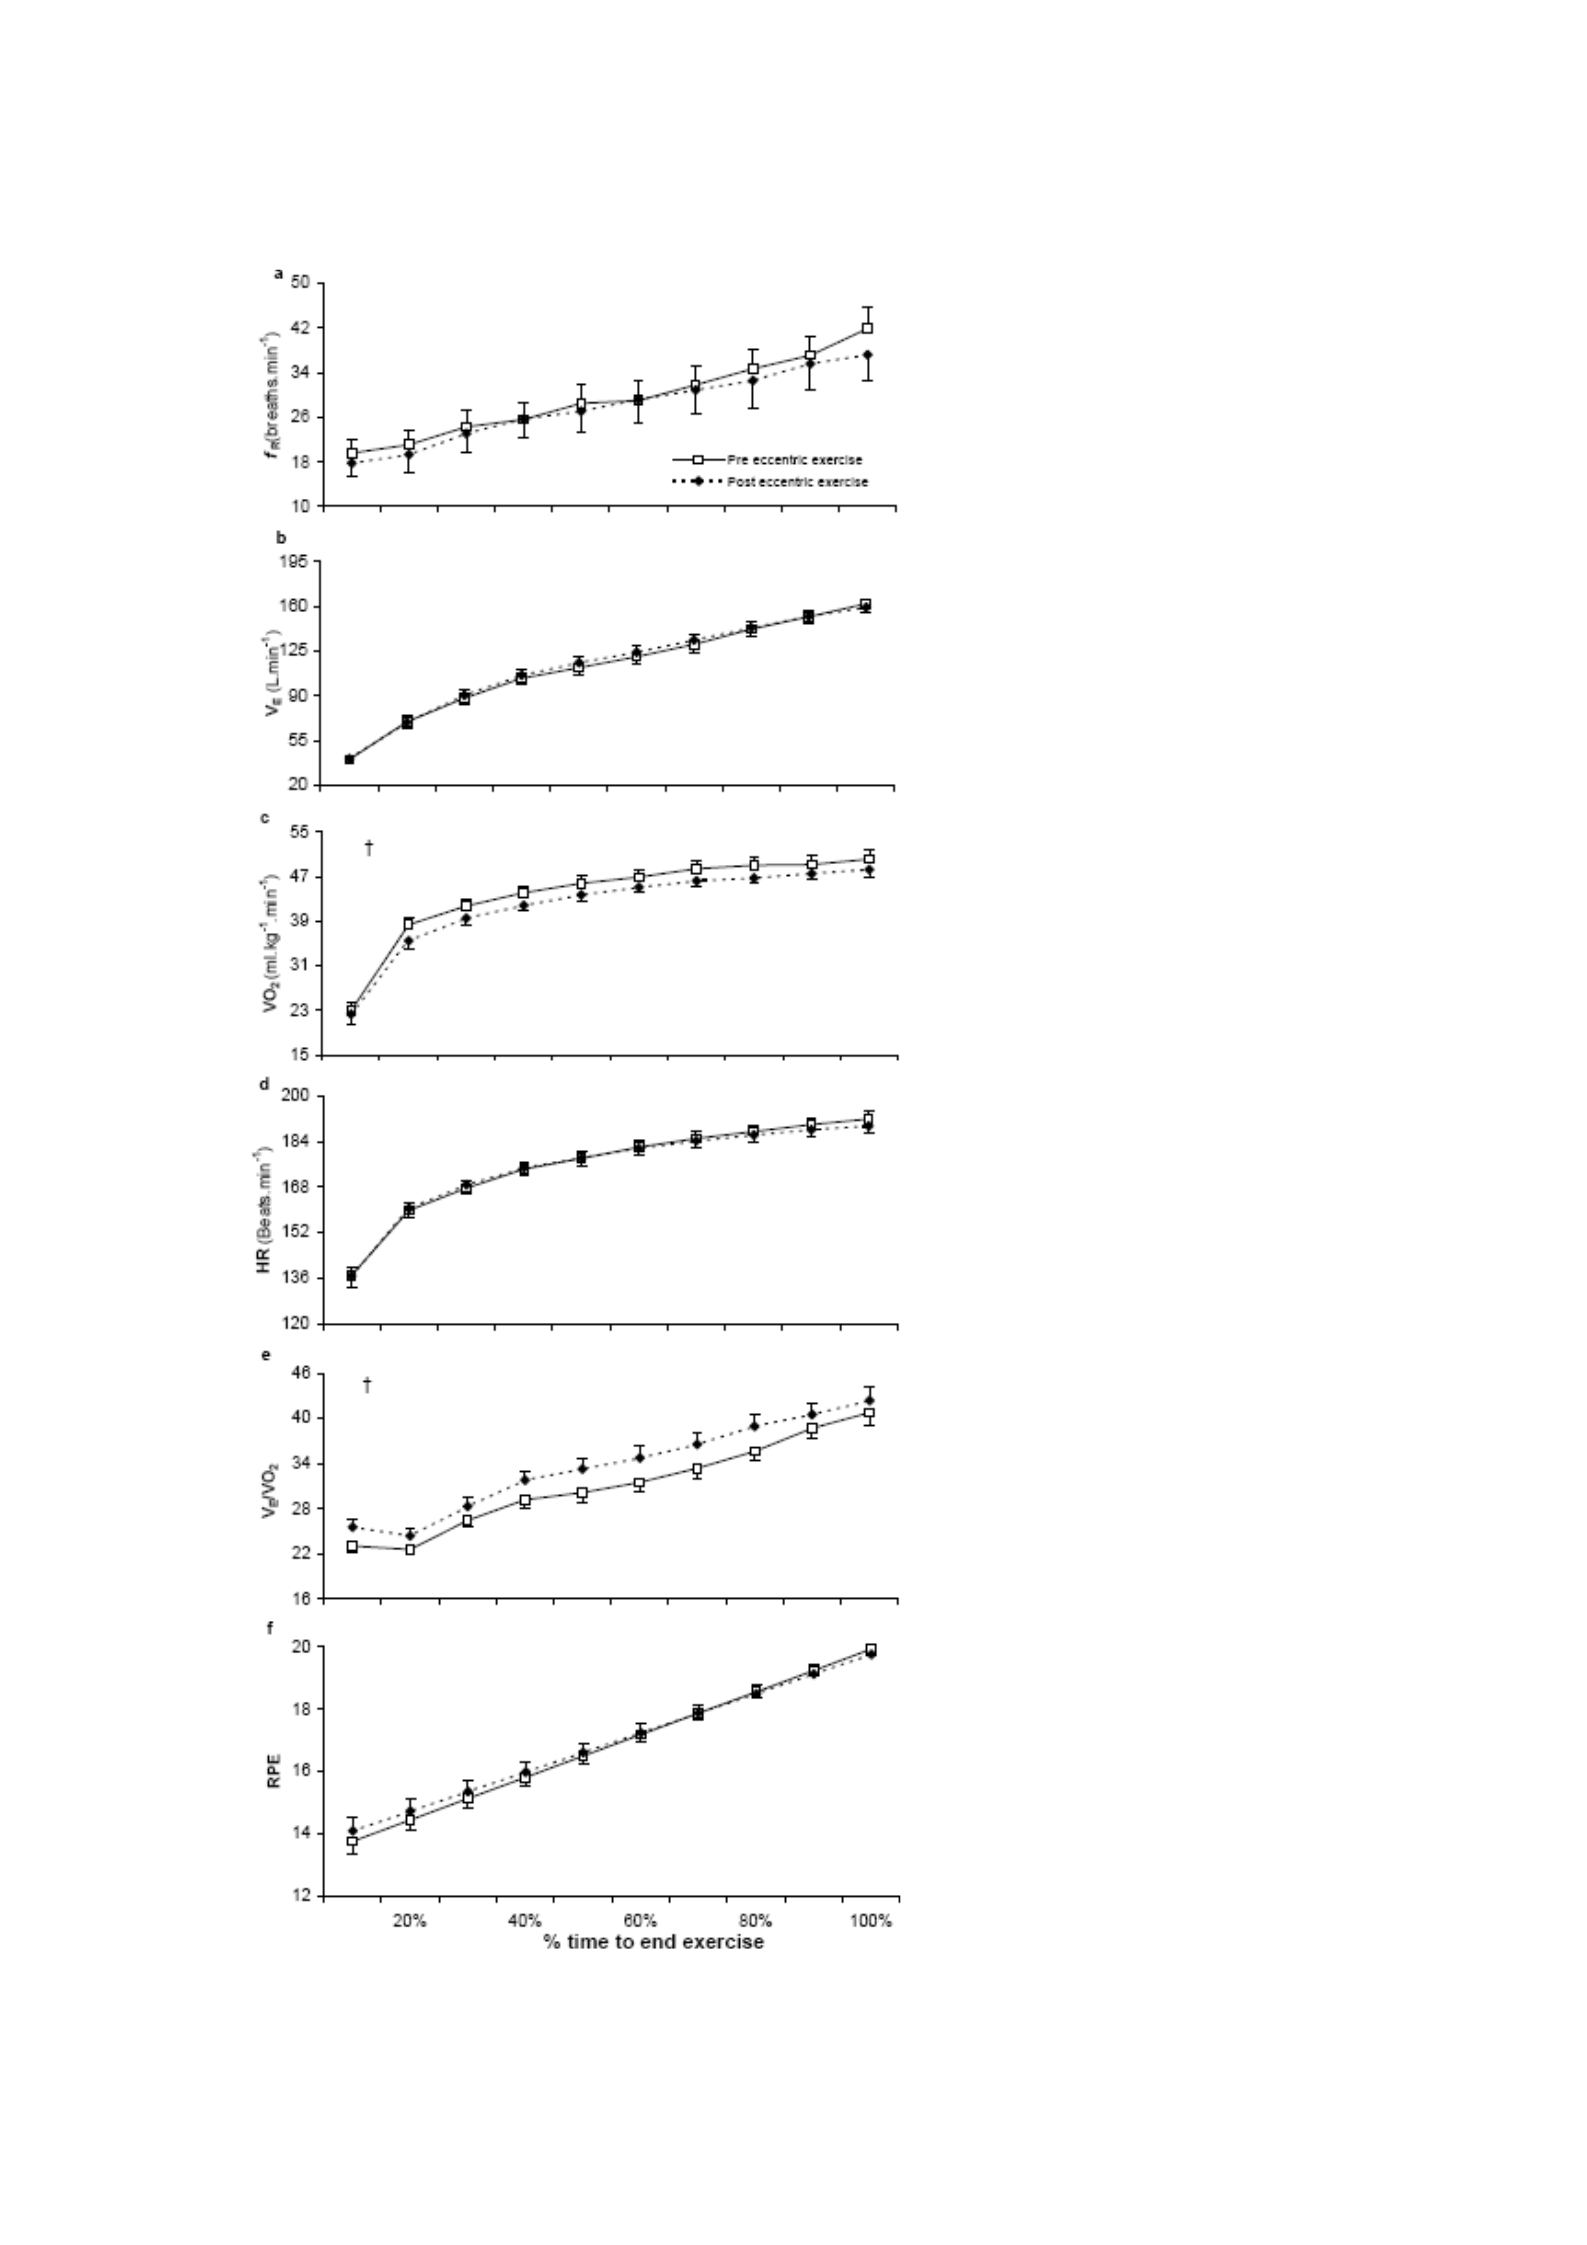
83
Figure 4.3
Percentage time values (severe
intensity exercise). Changes in a:
breathing frequency (fR), b: minute
ventilation ( V˙E ), c: oxygen
uptake
( V˙ O2 ), d: HR, e: V˙E /
V˙ O2
and f:
RPE during cycling at 70%∆ pre-
and 48h post-eccentric exercise set
against % time to volitional
exhaustion.
Values are mean (± SEM).
Significant effect for time for all
measures (P < 0.05).
† Significant main effect for test
(P < 0.05).
‡ Significant interaction effect
(test*time) (P < 0.05).
* Significantly different from pre
value (P < 0.05)

84
4.5 Discussion
This investigation demonstrates that a prior bout of eccentric, muscle-damaging exercise
augments the ventilatory response not only during severe intensity (70% ∆) cycle exercise
but also during moderate intensity (80% GET) cycle exercise. In addition, this study shows
that the perception of exertion is elevated during severe intensity exercise but appears to be
unaffected by a prior bout of eccentric exercise during moderate exercise.
Markers of muscle damage
As anticipated, the squatting protocol was effective in provoking changes in the markers of
muscle damage in all participants. The significant decreases in peak torque observed
following eccentric exercise concur with previously reported findings (Byrne et al., 2001).
Perceived muscle soreness was elevated above baseline measures at 30 min after the
eccentric exercise with the highest values reported at 48 h. These findings are consistent
with the previously reported characteristic temporal profile of increased muscle soreness
following eccentrically-biased exercise (e.g. Twist & Eston, 2005). As expected, the time
course of the CK response did not reflect the alterations in muscle function or perceived
soreness (Warren et al., 1999). However, the CK efflux, which was greatest at 24 h, does
provide indirect evidence of increased myocyte membrane permeability (Allen et al., 1995).
A rapid rise and peak in CK activity similar to that observed herein has previously been
observed following a similar eccentric exercise protocol (100 squats @ 70% body mass,
Byrne & Eston, 2002a).
Exercise test measures
The elevated ventilatory response to severe intensity cycle exercise observed in this study
concurs with previously reported observations during high-intensity, fixed-load cycle

85
exercise following muscle-damaging exercise (Gleeson et al., 1995; Schneider et al., 2007).
However, the observation that V˙
E
and fR were also increased during moderate intensity
exercise (<GET) was unexpected. Using a similar squatting protocol, which produced
comparable levels of strength loss (-14% at 48 h) and an exercise intensity of 62% V˙ O2max
Moysi et al. (2005) reported no change in ventilation or HR. In contrast, increases in both
ventilation and HR were observed in the present study, despite the fact that subjects
exercised a considerably lower intensity, 80%GET, equivalent to ~27% V˙ O2max for these
individuals.
The elevated ventilatory response observed whilst exercising with EIMD or DOMS has
been associated with alterations in metabolic factors. Specifically, it has been assumed that
an increase in [La] contributes to an augmented ventilatory response. The elevated [La]
may result from an increased dependence on type II fibres and a corresponding shift to
increased glycolytic energy production following muscle-damaging exercise (Braun &
Dutto, 2003; Chen et al., 2007b; Gleeson et al., 1995). However, no such change in [La]
was observed in the current study at either exercise intensity. Importantly, the observation
that the ventilatory response following EIMD is higher during exercise below GET
suggests that the altered exercise response may not be due to changes in metabolic factors.
In support of this proposition, Schneider et al. (2007) observed that phase II V˙ O2 kinetics
were not altered by DOMS and concluded that elevated [La] did not result from altered
oxidative function. Rather, these authors suggested that higher levels of [La] arose from an
increased rate of lactate efflux from damaged myocytes due to increased membrane
permeability. However, the higher rate of lactate efflux may be countered by enhanced
clearance
facilitated
by
increased
muscle
blood
flow
(Laaksonen
et
al.,
2006)
and

86
accordingly elicit an unchanged [La] response. Whilst the putative influence of [La] on the
ventilatory response should not be dismissed; in light of the findings of this study, other
potential stimuli demand consideration.
The increases in V
˙
E
and fR observed in the present study during moderate and severe
intensities and in V˙E / V˙ O2 during severe intensity may be attributed to alterations in
neural factors. The complex mechanisms involved in ventilatory control during exercise
involve a combination of central command and afferent feedback but these are poorly
understood. However, ventilation is known to increase in response to painful stimulation
(Haouzi et al., 2004). Thus the local muscle pain which occurs as a result of eccentric
exercise, such as observed in the present study, would be expected to have a stimulatory
effect on ventilation. It has been proposed that group III and IV afferent fibres located in
and around the blood vessels of exercising muscle are involved in modulating the ventilatory
response (Haouzi et al., 2004). Distension of these blood vessels, such as the changes
in the capillary lumen shape observed by Kano et al. (2005) following eccentric exercise,
would provoke a discharge from the afferent fibres leading to an increase in ventilation.
Thus, neural monitoring of peripheral vascular and local muscular events may, in part,
account for the augmented ventilatory response observed. Hotta et al. (2006) suggested
that changes in neural factors contribute not only to an enhanced ventilatory response but
also to alterations in force generation. Following eccentric exercise increased motor unit
activation may be necessary in order to achieve a given sub-maximal force (Semmler et al.,
2007). Similarly, a greater sense of effort is reported when producing a specific force
following eccentric exercise (Proske et al., 2004).

87
Consistent with these observations, subjects in the present study reported higher ratings of
perceived exertion (RPE) during fixed-load, severe intensity cycle exercise following
eccentric exercise, although RPE appeared to be unchanged during moderate exercise.
Jameson and Ring (2000) have suggested that during cycle exercise, ratings of perceived
exertion are based on a combination of leg muscle pain and feelings of breathlessness.
Thus the increased leg muscle soreness experienced by participants in this study following
the eccentric exercise is likely to have provided an important peripheral cue to inform the
RPE response. Similarly, the increased ventilatory response may have provided an
important central cue. Although the relative contribution of various central and peripheral
cues is poorly understood, central cues may be less important than peripheral cues,
particularly during low intensity exercise (Mihevic, 1981; Hampson et al., 2001). It is of
interest to note that the increased muscle pain and the elevated ventilatory response
experienced by participants in the present study at 48h did not significantly influence the
perception of exertion during moderate intensity exercise. However, during severe intensity
exercise, where the central, ventilatory cues may play a more influential role in informing
the perception of exertion, RPE was elevated.
The higher perception of exertion reported in the severe exercise bout at 48h may account
for the reduction in time to end exercise. Elevated RPE has previously been associated
with reduced time-trial performance in running (Marcora & Bosio, 2007) and in cycling
(Twist & Eston, 2009). Furthermore, the amplified ventilatory response may contribute to
the premature termination of exercise. Acute respiratory muscle fatigue may have
increased the severity of locomotor muscle fatigue via a respiratory muscle metaboreflex

88
increase effort perception and further centrally-mediated reductions in motor output (Romer
& Polkey, 2008).
The complex interplay of central and peripheral fatigue factors is of great importance in
determining the duration of an individual participant’s exercise performance. However, the
participant’s decision to terminate exercise is ultimately a conscious behavior based on the
perception of alterations in sub-conscious homeostatic control systems (St Clair Gibson et
al., 2003). As such, the perception of exertion may be considered fundamental to the
individual exercise response when a participant is required to exercise to ‘volitional
exhaustion’. Pertinent to this is the observation that minute-by-minute differences in
perceived exertion values reported during severe exercise before and after eccentric
exercise are eliminated when expressed as a percentage of total exercise duration. Thus,
further evidence is provided to support the proposition that there is a scalar-linear
relationship between the rating of perceived exertion and exercise duration (Eston et al.,
2007, Crewe et al., 2008; Faulkner et al., 2008; Joseph et al., 2008). Furthermore, the
observation that the differences in V
˙
E
and fR are also eliminated when expressed as a
proportion of time to exhaustion may provide some insight into the cues that inform the
perceived exertion response when cycling at high-intensity after a prior bout of eccentric
exercise.

89
4.6 Conclusion
This is the first study to investigate the influence of muscle-damaging exercise on the
ventilatory and perceived exertion responses to cycling in specific exercise domains above
and below the gas exchange threshold. Findings suggest that there is a strong link between
the augmented ventilatory response to cycling following eccentric exercise and the higher
rating of perceived exertion reported during exercise above GET. Furthermore additional
evidence is provided to support the observation that perceived exertion scales with exercise
duration during exercise to exhaustion.

The contents of this chapter are currently under review for publication:
Davies RC, Rowlands AV, Poole DC, Jones AM and Eston RG. Exercise-induced
muscle damage dissociates the Lactate and Gas exchange thresholds. Currently under
review.
90
CHAPTER 5:
THE EFFECT OF ECCENTRIC EXERCISE-INDUCED MUSCLE DAMAGE
ON THE GAS EXCHANGE THRESHOLD

91
5.1 Abstract
We tested the hypothesis that exercise-induced muscle damage (EIMD) would increase the
ventilatory ( V˙ E ) response to incremental/ramp cycle exercise (lower the gas exchange
threshold), without altering the blood lactate profile thereby dissociating the gas exchange
and lactate thresholds. It was considered that this intervention might provide a broader
understanding of the mechanisms underlying the relationship between the GET and lactate
threshold (Tlac). Ten physically active men completed maximal incremental cycle tests
before (pre) and 48 h after (post) performing eccentric exercise comprising 100 squats with
a load corresponding to 70% body mass. Pulmonary gas exchange was measured breath-
by-breath and finger-tip blood sampled at 1-min intervals for blood [La] determination.
GET occurred at a lower work rate (pre, 136 ± 27 W; post, 105 ± 19 W, P< 0.05) and V˙
O2
(pre, 1.58 + 0.26; post, 1.41 + 0.14 l.min-1, P< 0.05) after eccentric exercise. However,
Tlac occurred at a similar work rate (pre, 161 ± 19 W; post, 158 ± 22 W, P> 0.05) and
V˙ O2
(pre, 1.90 ± 0.20 l.min-1; post, 1.88 ± 0.15 l.min-1, P > 0.05) after eccentric exercise.
These findings demonstrate that EIMD dissociates the V˙ Eresponse to incremental/ramp
exercise from the [La] response indicating that V˙ Emay be controlled by additional or
altered neurogenic stimuli following eccentric exercise. Thus, due consideration of prior
eccentric exercise should be made when using the gas exchange threshold to provide a non-
invasive estimation of the lactate threshold.

92
5.2 Introduction
During dynamic incremental or ramp exercise protocols expired carbon dioxide production
( V˙ CO2 ) increases disproportionately as a function of V˙ O2 above what has been termed
the gas exchange threshold (GET) (Beaver et al., 1986). Traditionally, the GET has been
considered to result from an obligatory increase in non-metabolic CO2 production (and
associated increases of ventilation, ( V˙ E ) due principally to plasma bicarbonate buffering
of lactic acid-derived H+ (Beaver et al., 1986; Wasserman et al., 1990). Thus, identification
of the GET provides the basis for the non-invasive estimation of the lactate threshold (Tlac)
(Beaver et al., 1986; Caiozzo et al., 1982; Wasserman et al., 1973, 1990). However, the
V˙ E and
lactate
responses
to
incremental
exercise
have
been
dissociated
by
various
experimental and clinical conditions including exercise training (Poole & Gaesser, 1985),
glycogen depletion (Hughes et al., 1982; Sabapathy et al., 2006) and McArdle’s disease
(Hagberg et al., 1982; Paterson et al., 1990; Riley et al., 1993). In contrast, in a recent
study dichloroacetate (DCA) was reported to reduce both blood lactate [La] and V˙ E
during
incremental exercise thereby supporting the existence of a causal link between bicarbonate
buffering of lactic acidosis and increases in
V˙ E (Wilkerson et al., 2009). Today it is
appreciated that a wide variety of humoral and neural control mechanisms (central
command, afferent feedback from carotid body chemoreceptors and from contracting
muscles) contribute to the
V˙ E response to incremental/ramp exercise (Dempsey et al.,
2006; Haouzi, 2006; Haouzi et al., 2004; Waldrop & Iwamoto, 2006). While a complex
integration of these mechanisms is understood to mediate the V˙ E
response, it is likely that
under different conditions the proportional contribution of each of these might change.

93
During rhythmic exercise, group III and IV afferents are known to provide some V˙ E
drive
via mechanical stimuli such as local muscular distortion, vascular distension and increased
intramuscular pressure as well as via local humoral mediators including H+, lactate and
bradykinin (Ward, 2000; Whipp et al., 1981). Eccentric exercise causes profound muscle
structural and functional perturbations collectively referred to as exercise-induced muscle
damage (EIMD) (Clarkson et al., 1992). EIMD augments discharge from group III and IV
afferents (Avela et al., 1999; Komi, 2000; Taguchi et al., 2005) and this, rather than
elevated blood lactate concentration which is not an obligatory consequence of EIMD
(Twist & Eston, 2009), most probably contributes to the greater V˙ E
response to constant-
load cycle exercise evoked by EIMD (Gleeson et al., 1995; Schneider et al., 2007; Twist &
Eston, 2009) (Chapters 4).
The influence of a prior bout of eccentric exercise and the resultant EIMD on the V˙ E
and
gas exchange responses to incremental exercise has received very limited attention. Only
one previous study examined physiological responses to maximal incremental cycling;
unfortunately the bench-stepping protocol utilised in that investigation produced only mild
soreness (Gleeson et al., 1998). Thus, that bench-stepping protocol (Gleeson et al., 1998)
may not have increased the discharge from group III and IV afferents as much as a
procedure designed specifically to induce more severe EIMD. To our knowledge, the
influence of eccentric muscle-damaging exercise on the GET has not been investigated
previously. It is our contention that an eccentric exercise protocol such as that utilised
previously in our laboratory (Chapter 4) is likely to exacerbate the V˙ E response to

94
incremental/ramp exercise and, in so doing, potentially dissociate the V˙ E , gas exchange
and lactate responses.
It was the purpose of this investigation to determine the influence of EIMD on the GET and
Tlac responses determined during ramp exercise. Specifically, we tested the hypothesis
that completion of 100 squats (performed as 10 sets of 10 reps at ~ 70% body mass) would
augment the V˙ E
response (lower the GET) to subsequent incremental/ramp exercise in the
absence of an altered blood lactate profile thereby dissociating the GET from the lactate
threshold. It was speculated that this intervention might provide mechanistic insights into
the relationship between lactate accumulation and ventilatory control in the presence of
overt muscle damage.
5.3 Methods
Subjects
Ten healthy, physically active male subjects (age, 25 ± 7 years; mass, 80.1 ±9.9 kg; height,
1.80 ± 0.08 m) volunteered to participate in this study. All participants were asymptomatic
of illness and pre-existing injuries and had not performed any resistance training of the
lower limbs within the previous 6 months. Participants provided written informed consent
to participate in the study which was approved by the Ethics Committee of The School of
Sport and Health Sciences at The University of Exeter (See appendices B, C and D for
exemplar participant information sheet, participant consent form and ethical approval
certificate).

95
Experimental Design
Ramp incremental exercise test
Participants performed two ramp incremental exercise tests to volitional exhaustion on an
electronically-braked cycle ergometer (Lode Excalibur Sport, Groningen, The Netherlands)
(Figure 5.1). Each participant’s preferred seat height and handlebar positions were
recorded during their first test and replicated in the subsequent test. The height and mass
(SECA, UK) of each participant was also recorded. Exercise tests were performed at the
same time of day ± 1 h for each participant, before and 48 h after performing eccentric,
muscle-damaging exercise. Following 3 min of unloaded baseline cycling, the work rate
was increased in a ramp fashion by 1 W every 2 s (30 W.min−1) until the subject was
unable to continue despite receiving strong verbal encouragement. The participants were
required to maintain a pedal rate of 80 rpm during both incremental tests.
Figure 5.1 A participant performing a ramp incremental cycle exercise test.

96
Eccentric, muscle-damaging exercise protocol
Participants completed 100 (Smith) squats, performed as 10 sets of 10 repetitions with the
load on the bar corresponding to ~70% of each participant’s body mass. For further details
of this procedure please refer to Chapter 3.
Measurements
Assessment of muscle damage
All indicators of muscle damage (perceived muscle soreness (using a 0-10 visual analogue
scale (VAS)), creatine kinase (CK) activity and isokinetic peak torque (30 deg.s-1)) were
measured in the order listed, immediately before, 30 minutes after and 24 and 48 h after
performing the eccentric, muscle-damaging exercise protocol. For further details of these
procedures please refer to Chapter 3.
Ramp incremental exercise
Throughout the cycle exercise tests, before and 48 h after the muscle-damaging protocol,
pulmonary gas exchange was measured breath-by-breath via an online gas analysis system
(Cortex MetaLyzer 3B, Biophysik, Leipzig, Germany). Participants wore a nose clip and
breathed through a low-dead-space, low-resistance mouthpiece. Gas exchange was
measured throughout the tests using the Cortex Metasoft 3.1 software. The system was
calibrated prior to every test in accordance with manufacturer’s guidelines against known
concentrations of cylinder gases (15% oxygen, 5% carbon dioxide) and a three litre
calibration syringe (Hans Rudolph, Kansas City, USA) for gas flow. Inter-test coefficients
of variation for V˙
E ,
V˙
O2
and V˙
CO2
responses using this equipment in our laboratory

97
were 4.1%, 3.1% and 4.2% (for V˙ E , V˙ O2 and V˙ CO2 , respectively).

98
The gas exchange data sets were blind reviewed in order to determine the V˙ O2 peak and gas
exchange threshold (GET).
The V˙ O2 peak was determined as the highest 30-s average value
recorded before the participant’s volitional termination of the test. The GET was
determined from a cluster of measures which included 1) the first disproportionate increase
in CO2 production ( V˙ CO2 ) from visual inspection of individual plots of V˙ CO2 versus
V˙ O2 (V-slope method (Beaver et al., 1986)) and 2) an increase in the ventilatory
equivalent for O 2
( V˙ E / V˙ O2 ) with no concomitant increase in the ventilatory equivalent
for CO2 ( V˙ E / V˙ CO2 ) (Caiozzo et al., 1982).
Heart rate was monitored continuously using a wireless chest strap telemetry system (Polar
Electro T31, Kempele, Finland) and was recorded via a link to the Cortex gas analysis
system. Finger-tip blood samples were collected into a capillary tube immediately before,
after and at 1-min intervals during each incremental exercise test. Samples were
subsequently analysed for whole blood lactate (YSI 2300 Sport, Yellow Springs, Ohio,
USA). The blood lactate concentration [La] data sets were blind reviewed in order to
determine the lactate threshold (Tlac). Tlac was determined as the V˙ O2 associated with
the work rate prior to the first clear and sustained increase in [La] above resting levels from
visual inspection of individual plots of [La] vs. V˙ O2 .
Subjects were also asked to report their rating of perceived exertion (RPE) at 1-min
intervals throughout the incremental tests.
All subjects were familiarized with the Borg 6-

99
20 RPE scale and provided with standardised instructions on how to employ the scale prior
to testing (see Appendix F).
Statistical analysis
Indicators of muscle damage
Changes in the indicators of muscle damage (perceived muscle soreness, creatine kinase
activity and isokinetic peak torque) were analysed using a series of one-way repeated
measures analyses of variance (ANOVAs). Post-hoc Tukey tests modified for repeated
measures (Stevens, 2002) were run to determine where significant differences occurred. As
the CK activity data were not normally distributed these values were log-transformed prior
to statistical analysis (Twist & Eston, 2005) (see appendix H).
Ramp Incremental Exercise
Paired t-tests were used to determine significant differences in time to exhaustion, peak
values and gas exchange threshold (GET) and lactate threshold (Tlac) values pre- and post-
eccentric exercise. Further paired t-tests were used to determine significant differences in
physiological responses at the V˙
O2
corresponding to the pre-eccentric exercise GET.
Pearson’s product moment correlations were used to examine the relationship between
GET and Tlac values. All data were analysed using the statistical software package SPSS
for Windows (version 13) with statistical significance set at 0.05.

100
5.4 Results
Indicators of muscle damage
There were significant changes in all indicators of muscle damage following eccentric
exercise. Table 5.1 shows changes in muscle soreness, CK activity and isokinetic peak
torque before and after eccentric exercise.
Table 5.1
Changes in indicators of muscle damage. Mean ± SD values before (pre) and
at 30 min, 24 h and 48 h after eccentric exercise.
Measured variable pre 30 min 24 h 48 h
Soreness (1-10 VAS) 0.4 ± 0.4 4.4 ± 2.2* 5.8 ± 2.0* 6.4 ± 3.0*
CK activity (U/L) 180 ± 61 224 ± 103 637 ± 413* 350 ± 151*
Peak Torque (N.m) 30 deg.s-1 300 ± 53 240 ± 68* 248 ± 62* 254 ± 72*
* significantly different from pre-eccentric exercise value (P < 0.05).
Muscle soreness increased 30 min after eccentric exercise with the highest values reported
at 48 h (F (3, 27) = 21.01 P < 0.001). CK activity increased after eccentric exercise, with the
highest values observed at 24 h (FGG (1.38,12.39) = 9.61 P < 0.05). Isokinetic peak torque (30
deg.s-1) decreased by 20% at 30 min and was still 15% lower than baseline values at 48 h
(F (3, 27) = 17.96 P < 0.001).
Ramp Incremental Exercise
Peak values attained during the ramp tests pre- and post- eccentric exercise are shown in
Table 5.2. Time to exhaustion and associated WRpeak values were decreased following
eccentric exercise (t(9) = 2.62, P < 0 .05). There were no significant changes in V˙ E peak,
101
E
2
2
V˙ O 2
peak,
V˙ CO2 peak, HRpeak, RERpeak, [La]peak or RPEpeak (all P > 0.05). Table 5.3 shows
changes in variables associated with GET before and 48h after eccentric exercise. GET
occurred earlier and thus at a lower WR (t(9) = 3.74, P = 0.005) and V˙ O2 (t(9) = 2.57, P =
0.030). V˙ CO2 values at GET were also significantly lower (t(9) = 2.54, P = 0.032).
Table 5.2 Peak values attained during ramp exercise tests. Mean ± SD values before
(pre) and 48 h after (post) eccentric exercise
pre post
Time to exhaustion (s) 682 ± 71 635 ± 86*
WRPeak (W) 341 ± 36 318 ± 43*
V
˙
peak (l.min-1)
V
˙
O
peak
(l.min
-1
)
V
˙
CO
peak
(l.min
-1
)
HRpeak (beats.min-1) 182 ± 12 179 ± 13
RERpeak 1.35 ± 0.10 1.33 ± 0.12
[La]peak (mmol.l-1) 6.05 ± 1.36 5.64 ± 1.72
RPEpeak (Borg, 6-20 scale) 19.4 ± 0.5 19.1 ± 1.0
Peak minute ventilation ( V˙ E peak), V˙ O2 peak, V˙ CO 2 peak HRpeak and RERpeak were the highest 30s
average values attained during the ramp exercise tests.
* significantly different from pre-eccentric exercise value (P < 0.05).
145 ± 22 140 ± 35
3.34 ± 0.38 3.27 ± 0.35
4.47 ± 0.45 4.33 ± 0.56

102
Table 5.3 Values attained at the gas exchange threshold (GET) during ramp exercise
tests. Mean ± SD values before (pre) and 48 h after (post) eccentric exercise
pre post
Time (s) 262 ± 55 200 ± 37*
WR (W) 136 ± 27 105 ± 19*
V
˙
E
(l.min-1)34.2 ± 6.1 31.7 ± 4.6
-1
V
˙
O2 (l.min
)1.58 ± 0.26 1.41 ± 0.14*
V
˙
CO2
(l.min-1)1.35 ± 0.24 1.20 ± 0.18*
[La] (mmol.l-1) 1.71 ± 0.38 1.55 ± 0.21
RPE (Borg 6-20 scale) 10.5 ± 0.9 10.6 ± 1.4
* significantly different from pre-eccentric exercise value (P < 0.05).
Figure 5.2 shows the V˙ CO2 versus V˙ O2 (panel A) and blood [lactate] (panel B) responses
of a representative participant during ramp incremental exercise before and after eccentric
exercise; note GET is shifted to a substantially lower V˙ O2 after eccentric exercise whereas
Tlac is essentially unchanged. There were no significant differences in V˙ E , [La] or RPE
at GET before and 48h after eccentric exercise (P > 0.05).
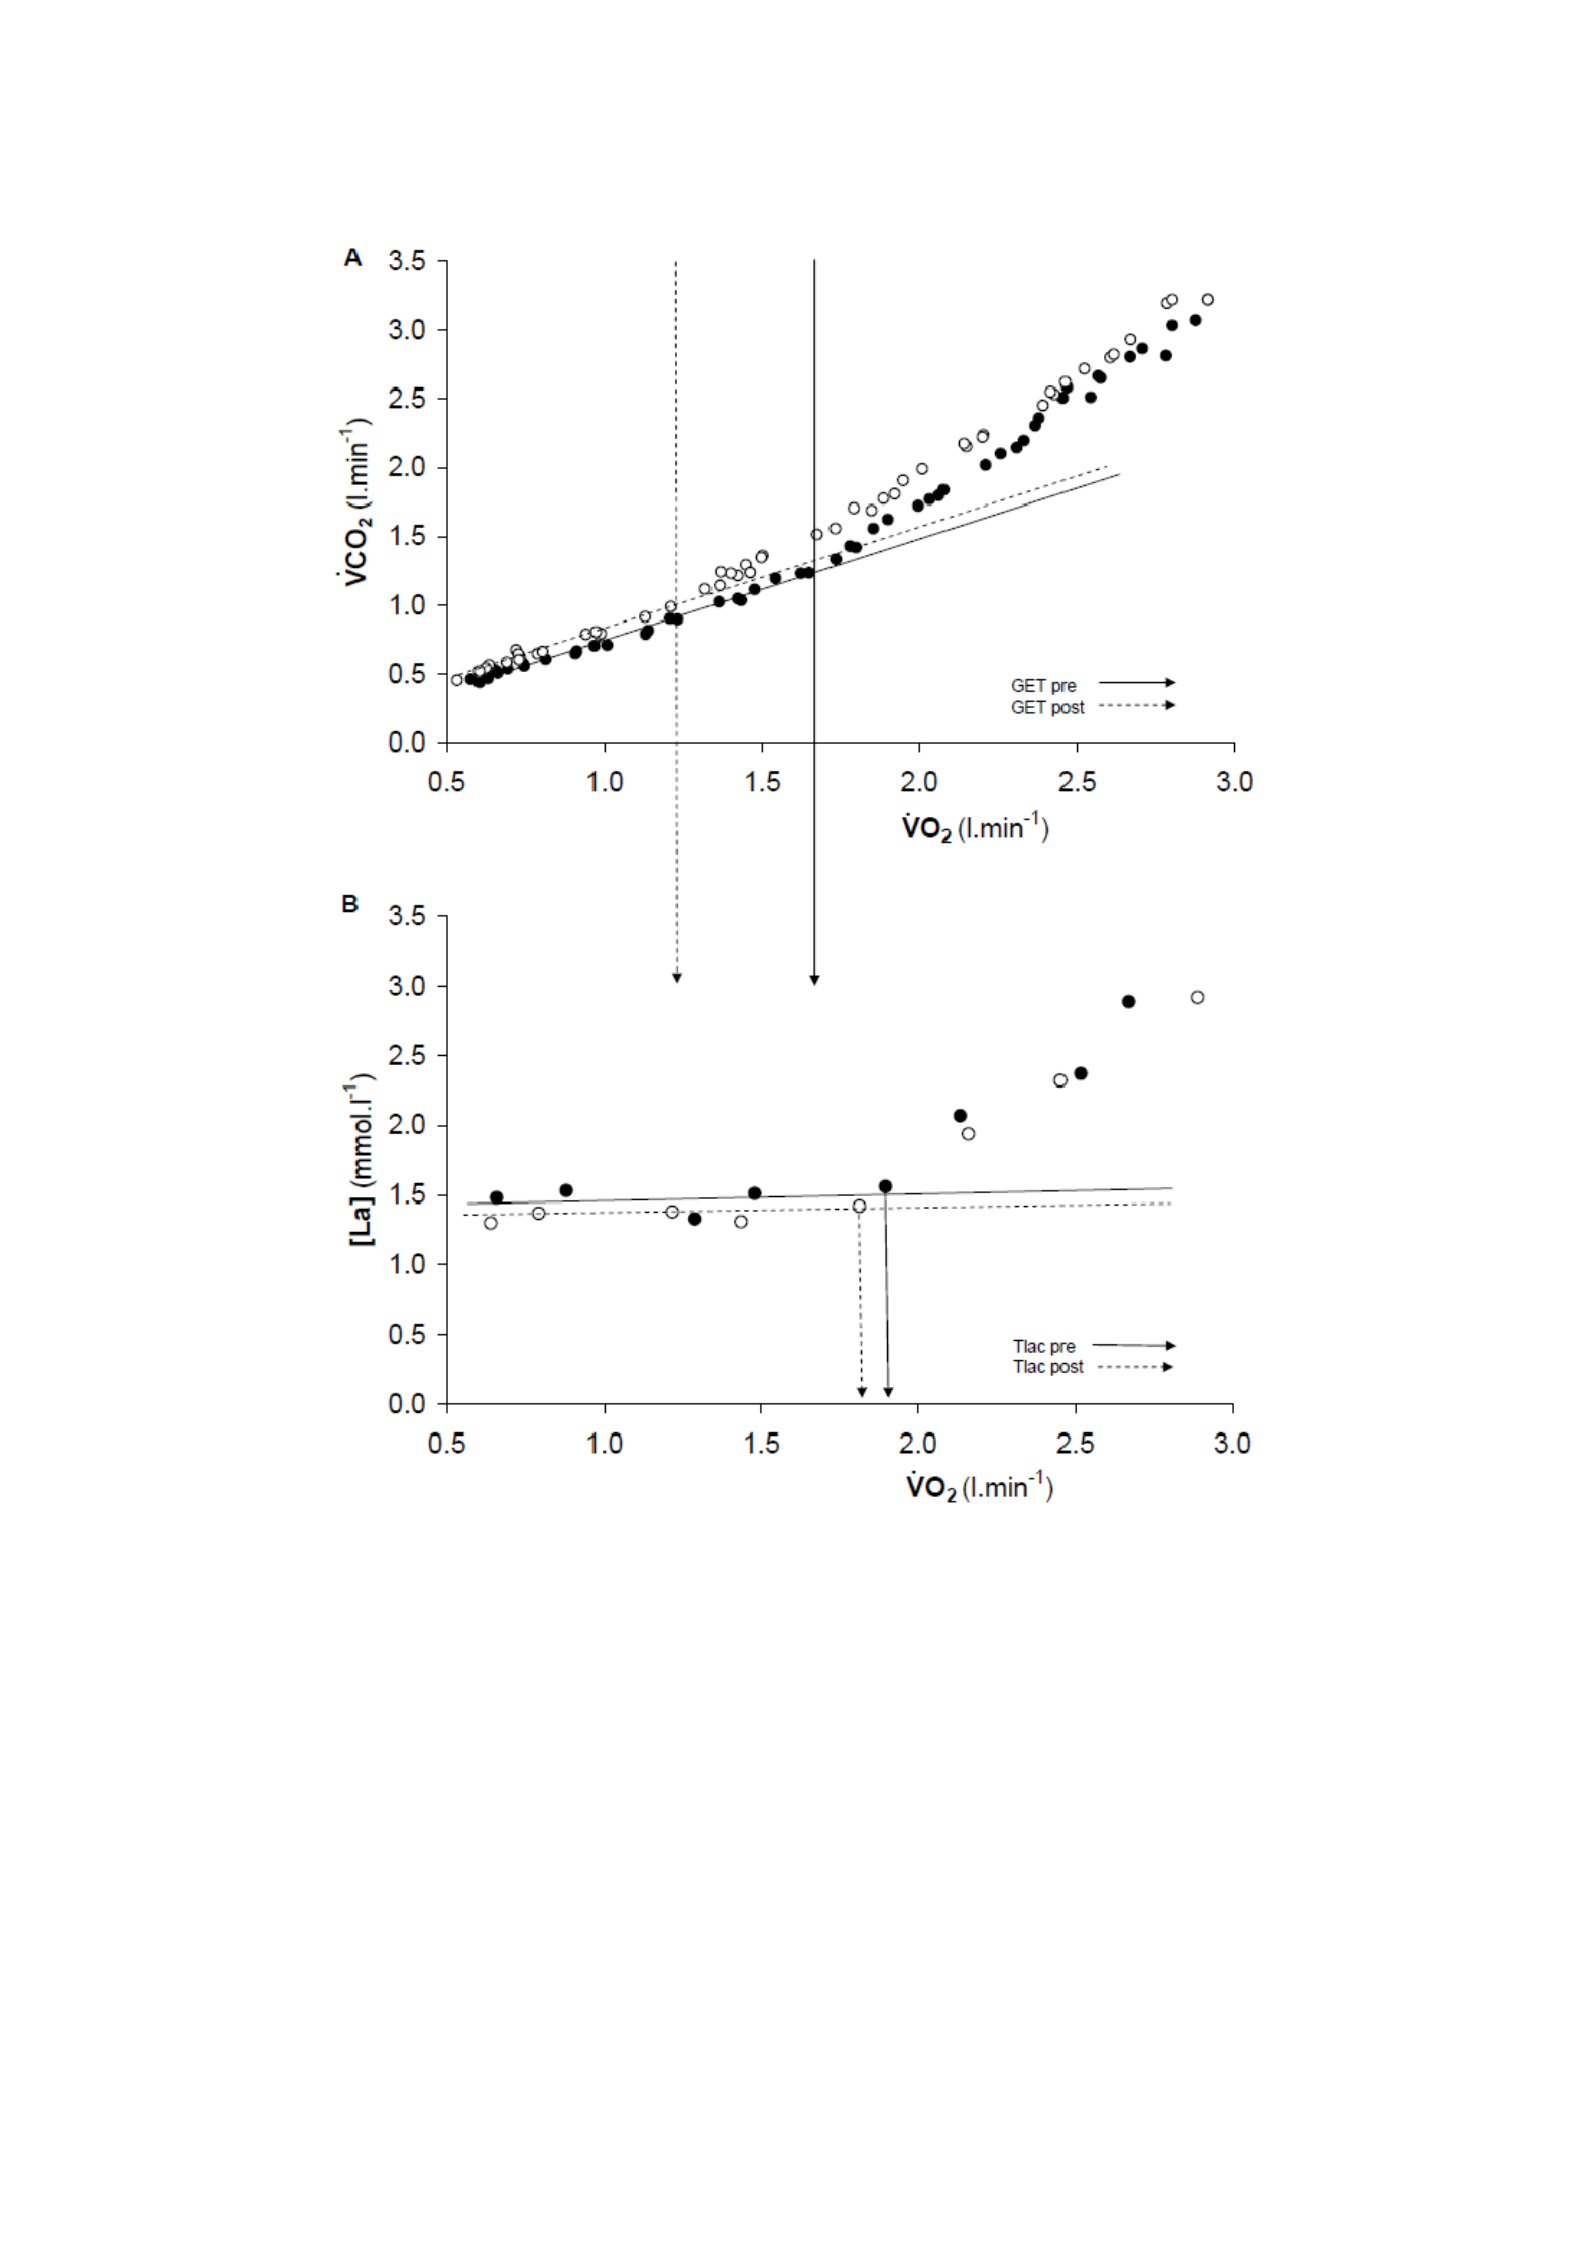
103
Figure 5.2 Representative response of V˙ CO2
vs
V˙
O2
(panel A) and blood [lactate]
(panel B) showing the region of interest, pre- (●) and 48 h post- (○) eccentric exercise
respectively. Best-fit S1 slopes and vertical arrows indicating the gas exchange threshold
(GET, panel A) and lactate threshold (Tlac, panel B) illustrate changes in the GET but not
the Tlac response, pre- (solid line) and post- (dashed line) eccentric exercise.
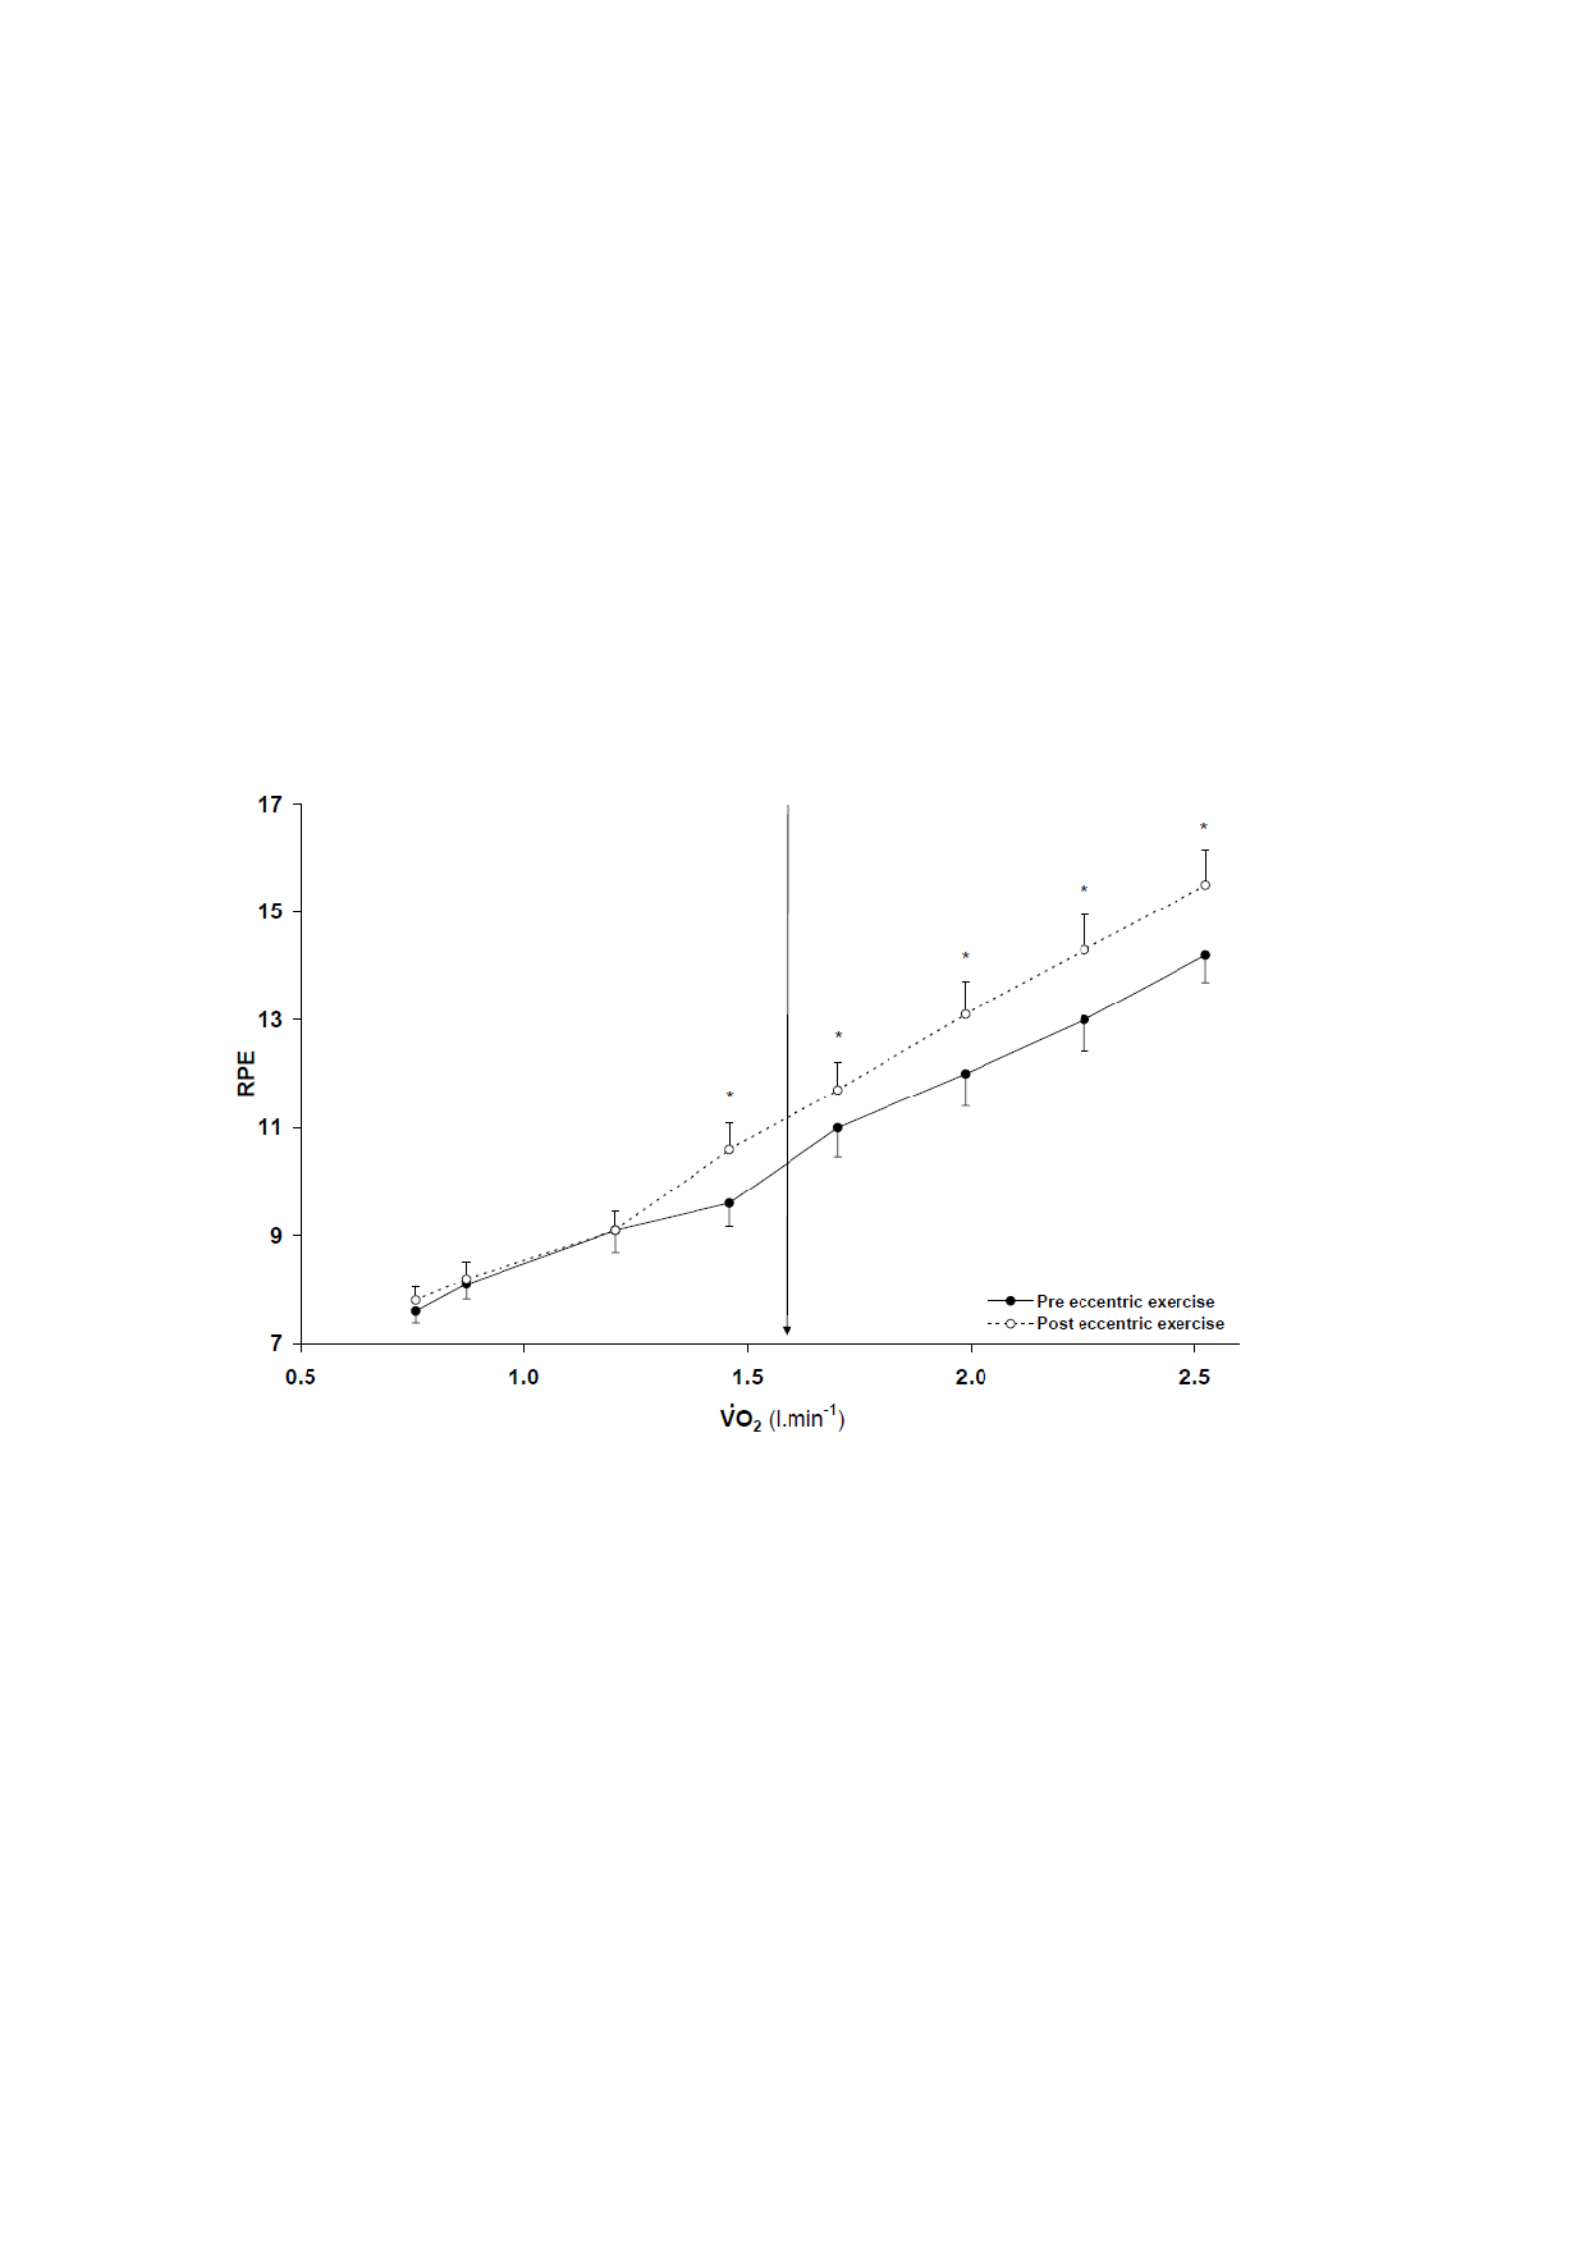
2
104
Figure 5.3 shows RPE responses before and after eccentric exercise. The Tlac occurred at a
similar work rate (pre, 161 ± 19 W; post, 158 ± 22 W, P> 0.05) and V˙ O2 (pre, 1.90 ± 0.20
l.min-1; post, 1.88 ± 0.15 l.min-1, P > 0.05) after eccentric exercise. The V˙ Oat GET was
significantly correlated with V˙ O2 at Tlac before (r = 0.78, P < 0.05) but not after eccentric
exercise (r = 0.50, P > 0.05).
There was no significant correlation between changes in
GET and Tlac values pre and post eccentric exercise (r = 0.53, P > 0.05).
Figure 5.3 Changes in ratings of perceived exertion (RPE) as a function of V˙ O2 , pre-
(●) and 48 h post- (○) eccentric exercise respectively. The vertical arrow indicates the gas
exchange threshold (GET) pre-eccentric exercise. There is a 7% increase (P < 0.05) in RPE
48 h post eccentric exercise at the V˙ O2 value of the pre-eccentric exercise GET.
* Significantly different from pre-eccentric exercise value (P < 0.05)
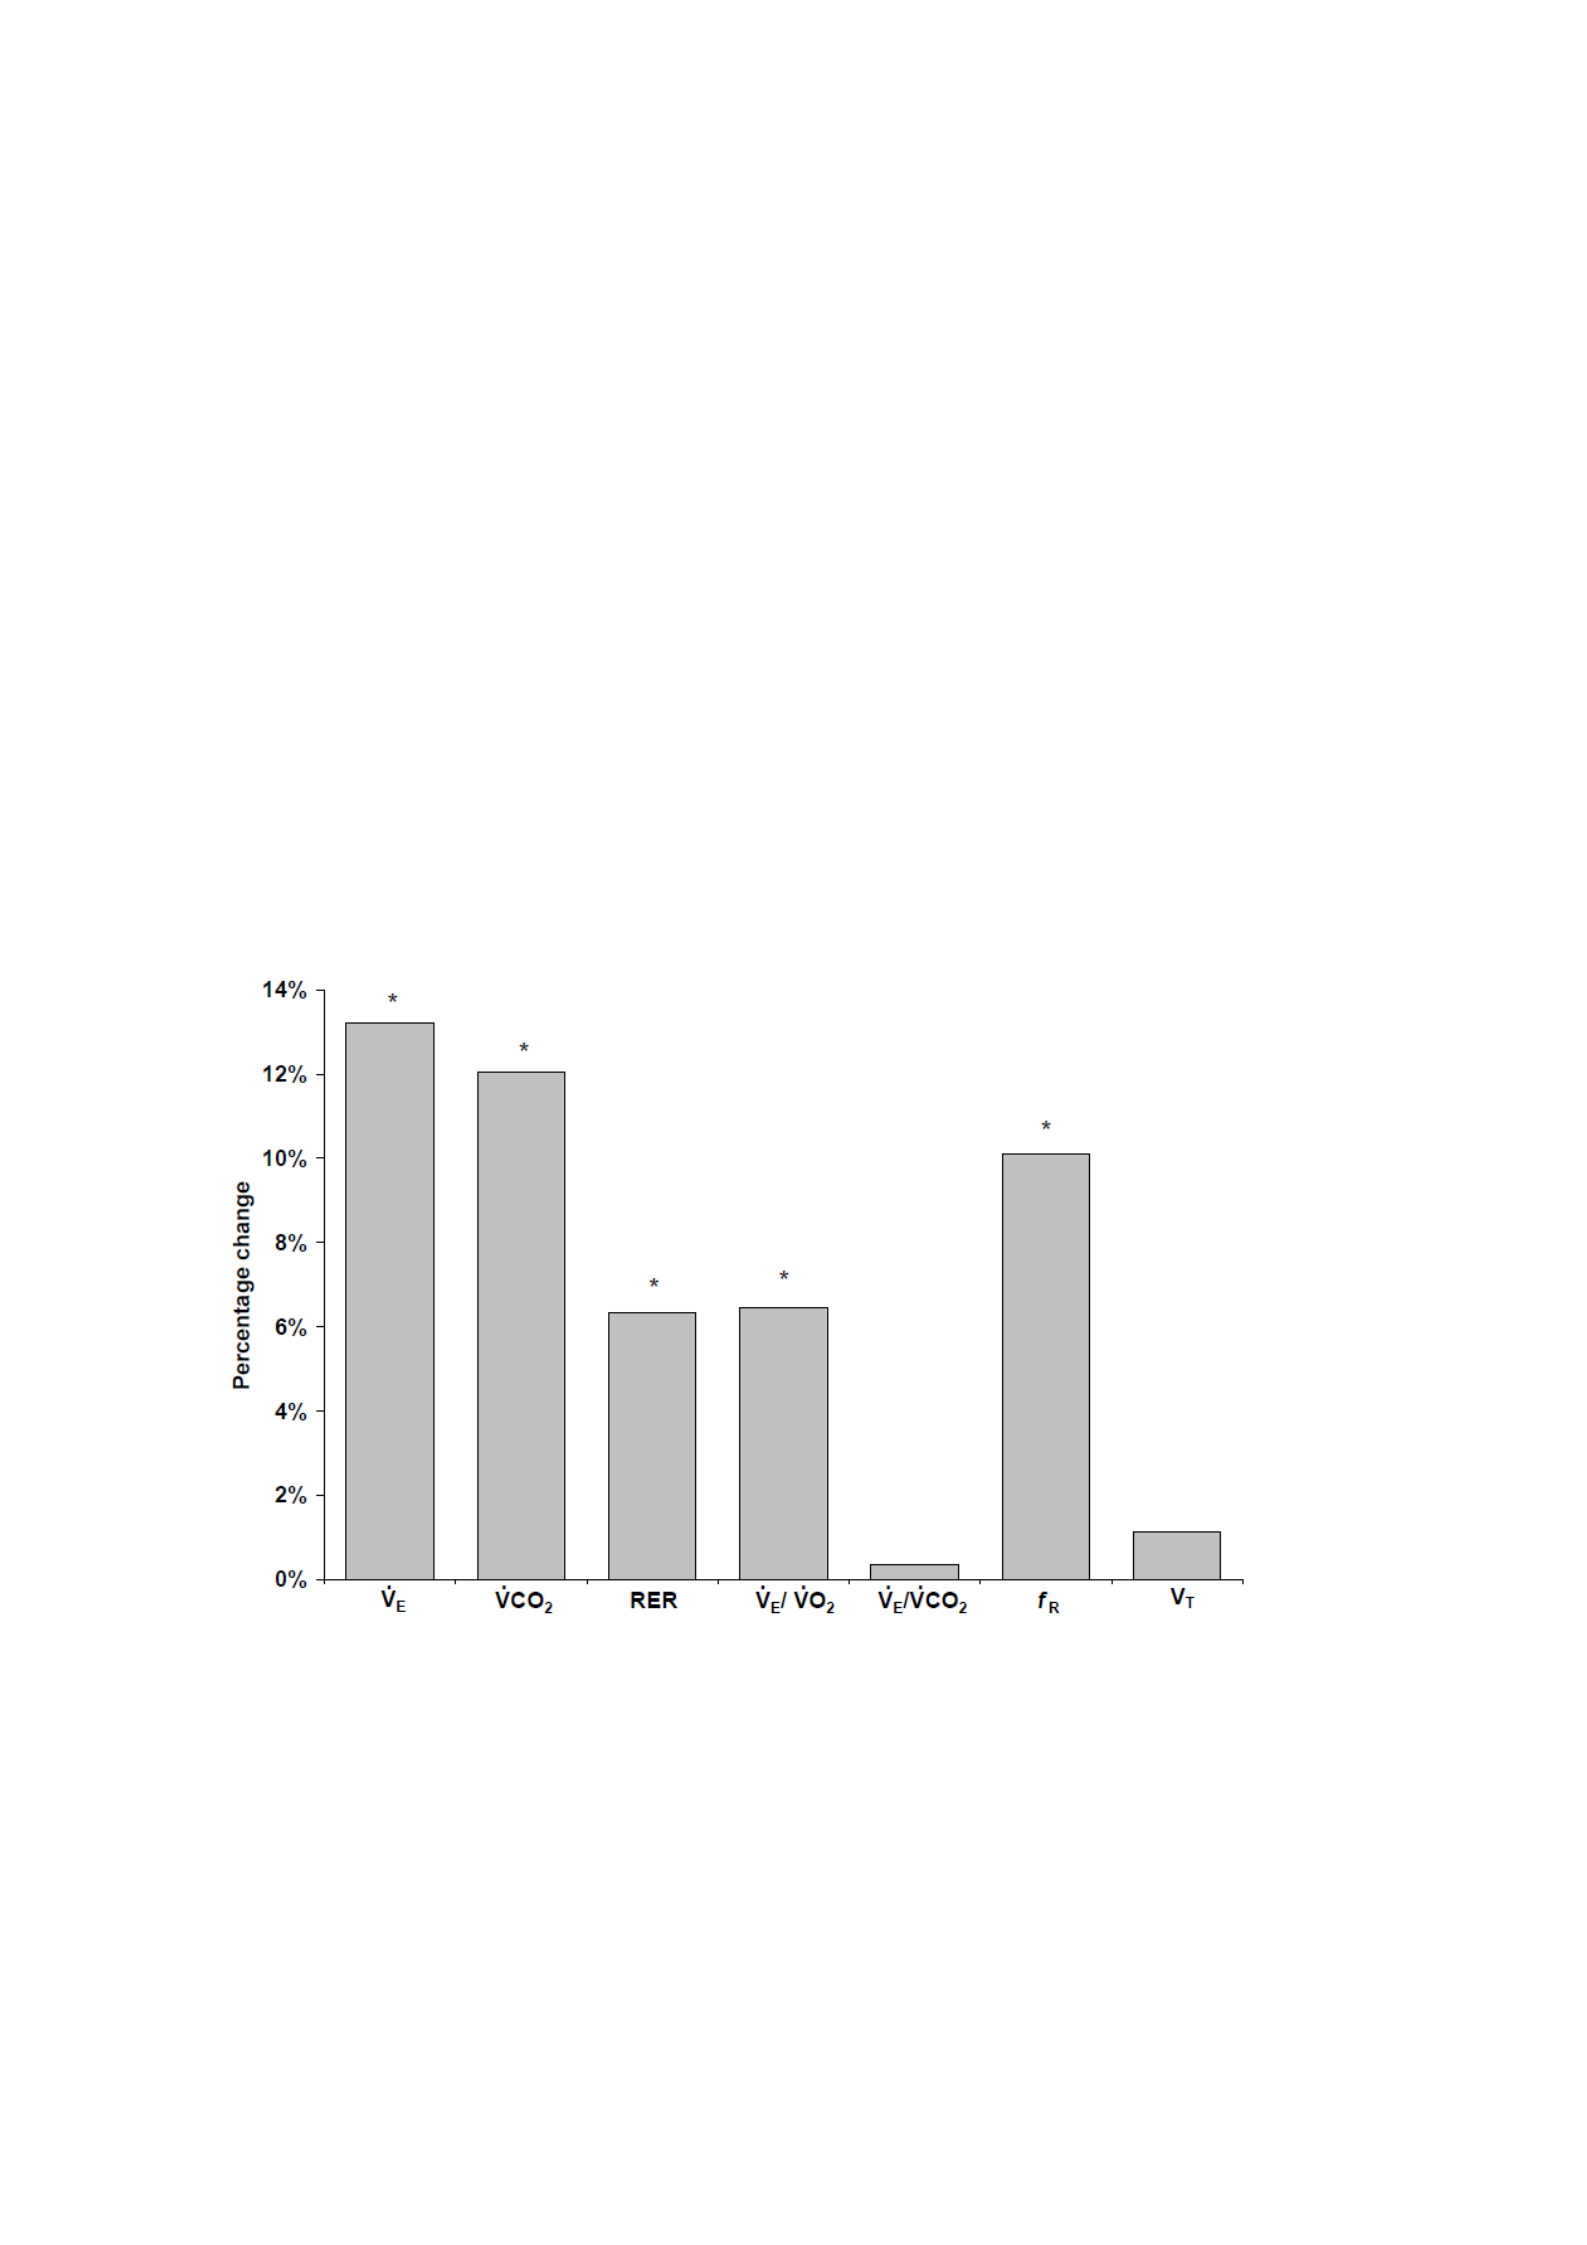
105
However, RPE increased significantly at the
V˙ O2
corresponding to the pre-eccentric
exercise GET. V˙ O2 was unchanged by the damage protocol and as anticipated, increased
as a linear function of work rate before and 48 h after eccentric exercise. A comparison of
responses before and 48 h after eccentric exercise at the V˙ O2 value at which pre-eccentric
exercise GET occurred revealed several significant differences (Figure 5.4).
Specifically,
there were increases in V˙ E
(t(9) = -2.88, P < 0 .05), V˙ CO2 (t(9) = -3.31, P < 0 .05), RER (t(9)
= -2.92, P < 0 .05), V˙ E / V˙ O2
(t(9) = -2.63, P < 0 .05), fR (t(9) = -2.49, P < 0 .05), and RPE
(t(9) = -2.40, P < 0 .05). There were no differences in V˙ E / V˙ CO2 , VT or [La] (P > 0.05).
Figure 5.4 Percentage changes in minute ventilation ( V˙ E ), expired CO2 ( V˙ CO2 ),
respiratory exchange ratio (RER), ventilatory equivalent for O2 ( V˙ E / V˙ O2
),ventilatory equivalent for CO2 ( V˙ E / V˙ CO2 ), breathing frequency (fR) and tidal
volume (VT) at the V˙ O2 value of the pre-eccentric exercise GET. Values are mean (±
SD).
* Significantly different from pre-eccentric exercise value (P < 0.05)

106
5.5 Discussion
The principal original finding of this investigation is that eccentric, muscle-damaging
exercise dissociates the V˙ E
and gas exchange responses to ramp incremental exercise from
the blood lactate response. While we believe these findings to be novel with respect to exercise-
induced muscle damage (EIMD), previous research has demonstrated that the GET and
lactate threshold (Tlac) may be dissociated by certain experimental protocols including
exercise training (Poole & Gaesser, 1985) and glycogen depletion (Hughes et al., 1982).
Thus our findings provide evidence to suggest that following eccentric exercise the control of
pulmonary ventilation is influenced by altered or additional stimuli, possibly of neurogenic
origin.
As anticipated, the [La] response to ramp incremental cycle exercise was not altered by the EIMD
intervention. This finding supports the contention that elevated blood [La] is not an
inevitable consequence of EIMD and is, therefore, unlikely to be linked causally to the
augmented V˙ E
response observed herein and elsewhere (Twist & Eston, 2009) (Chapter 4).
Instances of increased blood [La] following eccentric exercise have been linked with a putative
switch to more glycolytic energy production possibly as a result of an increased reliance on
type II motor unit recruitment (Braun & Dutto, 2003; Chen et al., 2007b; Gleeson et al.,
1995, 1998). However, it has been demonstrated that EIMD does not compromise skeletal
muscle oxidative function (Walsh et al., 2001) or alter pulmonary
V˙ O2 kinetics (Schneider et al., 2007).
Our findings contrast with those reported in the only previous study to investigate responses to
incremental exercise after eccentric exercise (Gleeson et al., 1998).
Gleeson

107
and co-authors (1998) reported no change in endurance time, V˙ O2 , V˙ E , or RER responses
but found [La] to be higher 48 h after completing a bench-stepping intervention which
provoked only mild soreness. Differences in the damage intervention, the incremental
protocol employed and the level of muscle soreness induced may account for the disparity
in V˙ E and [La] responses between investigations.
There was a small and statistically non-significant difference between the pre-eccentric
exercise work rates for the lactate and gas exchange thresholds, with the gas exchange
threshold occurring slightly earlier. It should be recognised that the dynamics of blood
lactate production and clearance (and hence appearance of lactate in the blood) may differ
from the more immediate stimuli for changes in gas exchange and ventilation during ramp
incremental exercise. Moreover, gas exchange was measured on a continuous breath-by-
breath basis whereas blood samples for [La] determination samples were collected at
discrete 1-min intervals. This may increase the potential for disagreement between the
lactate and gas exchange thresholds.
The cause and effect relationship between Tlac (cause) and GET (effect) is fundamental to
the traditional “anaerobic threshold” hypothesis (Beaver et al., 1986; Wasserman et al.,
1973, 1990).
However, certain experimental conditions have been demonstrated to elicit a
dissociation of [La] and
V˙ E responses. Under conditions of acute hypoxia (Ozcelik &
Kelestimur, 2004) and following prior volitional hyperventilation (Ozcelik et al., 1999)
GET is reduced in comparison to the normal, control condition, without a concomitant
decrease in Tlac.
It has been proposed that a ‘pseudo-threshold’ (Whipp, 1987) is evoked
by a ‘wash-in’ of CO2 to the depleted body stores (hyperventilation) or enhanced carotid

108
body chemosensitivity to CO2 (hypoxia). However, the reduction in GET observed in the
present study does not appear to result from humoral stimuli arising from alterations in
blood [La]. Previous investigations reporting a dissociation of V˙ E and [La] responses to
exercise have suggested that V˙ E
may have been influenced by differences or alterations in
the extent of neurogenic control. Patients suffering from McArdle’s disease, a condition
where
a
lack
of
muscle
phosphorylase
precludes
increases
in
[La]
during
exercise,
demonstrate a dissociation of V˙ E
and [La] responses during incremental cycling (Hagberg
et al., 1982; Paterson et al., 1990). Similarly, under conditions of reduced muscle glycogen
content (Hughes et al., 1982; Sabapathy et al., 2006) and following a period of exercise
training (Poole & Gaesser, 1985)
V˙ E and [La] responses to exercise are dissociated.
However, the existence of a causal link between bicarbonate buffering of lactic acidosis and
increases in V˙ E has recently been supported in a study which used DCA to reduce [La]
during incremental exercise (Wilkerson et al., 2009). While lactic acidosis may provide an
important stimulus to V˙ E
it is only one of many factors that can influence the V˙ E
response
and therefore modulate GET (Dempsey et al., 2006; Ward, 2000; Whipp et al., 1981). It
should be mentioned here that while under normal control conditions it is considered that
increased non-metabolic CO2 production from the bicarbonate buffering of lactic acidosis
stimulates the increased
V˙ E (Wasserman et al., 1973, 1990), in the present study the
relative hyperventilation following eccentric exercise might have increased
V˙ CO2
by
‘blowing off’ CO2 from the body stores (Ozcelik et al., 1999) thus reducing the GET as
established using the V-slope method (Beaver et al., 1986). Thus we speculate that the
augmented V˙ E
response and reduced GET observed herein likely result from non-humoral
stimuli originating in the damaged, exercising muscle.

109
The eccentric exercise protocol employed in this study is known to be effective in inducing
damage (Byrne & Eston, 2002a, 2002b) (Chapter 4). The primary event which leads to
muscle damage from unaccustomed eccentric exercise involves the disruption of
sarcomeres and myocyte membranes leading to dysfunction of the excitation-contraction
(E-C) mechanism (Proske & Morgan, 2001). As a consequence the immediate and
prolonged reductions in peak torque observed in the present investigation may reflect
damage to the E-C mechanism. Furthermore the significant increase in plasma CK activity
is indicative of increased membrane permeability. While EIMD does not appear to disrupt
intrafusal fibres as demonstrated by the unaltered sensitivity of muscle spindle or Golgi
tendon afferents (Gregory et al., 2002, 2004), the disruption to extrafusal fibres may
provide mechanical stimulation to fine myelinated (group III) and unmyelinated (group IV)
afferents (Avela et al., 1999; Komi, 2000; Taguchi et al., 2005).
These thin-fibre afferents
can exert a significant influence on V˙ E
during dynamic exercise (Matieka & Duffin, 1995)
and may have provided an important additional drive to V˙ E leading to the reduction in
GET observed in the present study. Similarly, structural and functional disruption to local
microvasculature following eccentric exercise (Kano et al., 2005) has been implicated in
augmenting the V˙ E response via stimulation of group III and IV afferents (Haouzi et al.,
2004). We have previously used an identical eccentric exercise protocol to that employed
herein to induce damage and have observed disruption in the matching of O2 delivery (
Q˙ O2 ) to O2 utilisation ( V˙ O2 ), consistent with such microvascular dysfunction,
in
conjunction with an augmented V˙ E response (Chapter 4) .

110
Muscular pain is understood to provide an important stimulus to the ventilatory response
via the mechanical stimulation of nociceptive muscle afferents (Duranti et al., 1991).
Excitation of these afferents via painful electrical muscular stimulation or ischemic muscle
pain elicits a reflex increase in breathing frequency (fR) and minute ventilation (Duranti et
al., 1991) whilst concurrently depressing the central neural drive to ventilation (Waldrop et
al., 1982). As the mechanical sensitivity of group III and IV thin fibre muscle afferents is
augmented by experimental muscle pain as detailed above, so it may be increased by the
mechanical hyperalgesia, the sensations of muscle tenderness and movement-induced pain,
that result from unaccustomed eccentric exercise.
Thus the soreness experienced by our
participants during muscle activation may have contributed to the augmented fR and V˙ E
observed following eccentric exercise via afferent neural reflexes.
The elevated ratings of perceived exertion (RPE) reported by our participants corroborate
previously reported findings during constant load cycle exercise after eccentric exercise
(Twist & Eston, 2009) (Chapter 4) and may account for the reduction in time to exhaustion.
This decrease and the associated reduction in WRpeak values are consistent with
observations of impaired endurance performance brought about by the effects of eccentric
exercise (Marcora & Bosio, 2007; Twist & Eston, 2009) (Chapter 4). Submaximal
differences in V˙ E , V˙ CO2 , RER and RPE during ramp exercise are resolved at maximal
exercise albeit at a lower work rate and exercise time. This observation supports the
proposition that the rating of perceived exertion scales with exercise duration (Crewe et al.,
2008; Eston et al., 2007; Faulkner et al., 2008; Joseph et al., 2008) and also that a strong
link exists between V˙ E and RPE responses to cycling following eccentric exercise (Chapter
4).

111
5.6 Conclusion
In conclusion, a prior bout of muscle damaging eccentric exercise augments the V˙ E
response to ramp incremental cycling leading to a reduction in GET in the absence of
altered blood [La]. The resultant dissociation between GET and Tlac indicates that the two
phenomena are not causally linked in the presence of EIMD.
We propose that the increase
in V˙ E
and reduction in GET 48 hours after muscle-damaging eccentric exercise are evoked
most likely by increased activation of group III and IV afferents stimulated via mechanical
disruption of muscle fibres and local microvasculature and are not the result of altered
blood [La].

The contents of this chapter are currently under review for publication:
Davies RC, Eston RG, Fulford J, Rowlands AV and Jones AM. Muscle damage alters
the metabolic response to dynamic exercise in humans: a 31P-MRS study. Currently
under review.
112
CHAPTER 6
THE 31P-MRS METABOLIC RESPONSE TO INCREMENTAL
EXERCISE FOLLOWING ECCENTRIC,
MUSCLE-DAMAGING EXERCISE

113
6.1 Abstract
This study used 31P-magnetic resonance spectroscopy (31P-MRS) in an attempt to reveal
any link between changes in muscle metabolism and the limitations to exercise tolerance in
humans with and without exercise-induced muscle damage (EIMD). Ten healthy,
physically active men performed incremental knee extensor exercise inside the bore of a
whole-body MRS before (pre) and 48 h after (post) performing 100 squats with a load
corresponding to 70% of body mass. Time to exhaustion was significantly reduced
following EIMD (519 ± 56 and 459 ± 63 s, pre and post EIMD, respectively). End exercise
pH (pre: 6.75 ± 0.04 post: 6.83 ± 0.04) and [PCr] (pre: 7.2 ±1.7 post: 14.5 ± 2.1 mM)
values were higher following EIMD (both P <.05). However, end exercise [Pi] was not
significantly different following EIMD (pre: 19.7 ± 1.9 post: 21.1 ± 2.6 mM, P > .05).
Resting [Pi] values (pre: 4.7 ± 0.8 post: 6.7 ± 1.7 mM) and consequently [Pi]:[PCr] values
(pre: 0.12 ± 0.02 post: 0.18 ± 0.05) were significantly elevated following EIMD and these
mean differences were maintained during incremental exercise (all P <.05). In contrast,
[PCr] and pH values were not different pre and post EIMD at rest or during incremental
exercise (all P >.05). Findings indicate that alterations in phosphate metabolism,
specifically increases in resting [Pi] that are maintained during exercise, may contribute to
the reduced exercise tolerance experienced with EIMD.

114
6.2 Introduction
Unaccustomed eccentrically-biased exercise results in substantial alterations to skeletal
muscle structure and function. Morphological changes include disruption of the
cytoskeleton, sarcolemma and T-tubules (Fridén and Lieber, 2001), and changes to
capillary geometry (Kano et al., 2004). The loss of sarcolemmal integrity results in an
efflux of intramyocyte proteins into the bloodstream (Hortobágyi & Denahan, 1989) and an
influx of extracellular Ca2+ into the sarcoplasm (Armstrong, 1984). These changes are
associated with an acute inflammatory response and delayed onset muscle soreness
(DOMS) (MacIntyre et al., 1996) and are collectively referred to as exercise-induced
muscle damage (EIMD).
Performance decrements associated with EIMD include a reduction in maximal force-
generating capacity (Clarkson et al., 1992) and a shorter time to exhaustion (Asp et al.,
1998; Carmichael et al., 2005, 2006). Carmichael et al. (2005, 2006) have reported
decreases in treadmill run time to fatigue in mice following a bout of downhill running.
The decline in performance was associated with increases in the inflammatory cytokine,
interleukin 1 β (IL-1β) within regions of the brain responsible for movement, motivation,
perception of effort and pain (Carmichael et al., 2005). Central fatigue factors such as the
enhanced production of inflammatory cytokines have also been implicated in reduced time
trial running (Marcora and Bosio, 2007) and cycling performances in humans (Twist and
Eston, 2009,) where an elevated perception of exertion appeared to mediate performance
following eccentric exercise. Peripheral fatigue factors originating within the damaged
muscle tissue may also be involved in the reduced time to exhaustion following eccentric,
muscle-damaging exercise.
Using muscle biopsy procedures, Asp et al. (1998) reported

115
decreases in muscle glycogen content in human subjects following muscle-damaging
exercise which were associated with a 23% reduction in maximal work capacity during
incremental knee extensor exercise. Other observed changes in metabolic function
following eccentric exercise include impaired muscle glycogen resynthesis (Asp et al.,
1995, 1998) and an elevated blood lactate response during exercise (Gleeson et al., 1995,
1998; Asp et al., 1998). It is feasible that these changes reflect a shift in the muscle
metabolic profile to an increased reliance on non-oxidative metabolism, contributing to the
decreased endurance capacity following EIMD (Asp et al., 1998). However, the precise
nature of the accelerated fatigue development experienced with EIMD is poorly
understood.
Non-invasive evaluation of muscle metabolism can be achieved using 31P-magnetic
resonance spectroscopy (31P-MRS). Several studies have used this technology to
demonstrate an increase in the resting inorganic phosphate (Pi) to phosphocreatine (PCr)
ratio following EIMD, suggestive of an increase in resting muscle metabolism (McCully
1992, Rodenburg et al., 1995; Lund et al., 1998a, 1998b). Several of the candidate
mechanisms for the accelerated development of fatigue and reductions in peak power
observed following eccentric exercise, including increases in Pi and ADP and decreases in
pH, can be measured using 31P-MRS. Rodenburg et al. (1995) reported no difference in the
Pi:PCr ratio, pH or peak power during graded knee extensor exercise performed 24 h after a
bout of stepping exercise designed to induce EIMD. However, the authors concluded that
the lack of change in several markers of muscle damage indicated that the muscle-
damaging protocol employed was not sufficiently severe to alter muscle metabolism
(Rodenburg et al., 1995).

116
It has been demonstrated that an effective muscle-damaging protocol reduces time to
exhaustion during high-intensity cycling (Chapter 4). However the mechanisms underlying
the reduced endurance capacity following muscle-damaging exercise remain to be
determined. Central mechanisms which may potentially influence the increased
development of fatigue, such as increased inflammatory cytokine production are difficult to
evaluate during dynamic exercise in the human model. Putative peripheral fatigue
mechanisms including an increased rate of [PCr] depletion, an increased accumulation of
[Pi] and [ADP] and a decreased rate of fall in pH can all be assessed using 31P-MRS.
Following a period of endurance training, incremental knee extensor exercise tolerance is
enhanced with the relationships of [Pi]:[PCr], [PCr] and pH against time demonstrating a
rightward shift (Jones et al., 2007). It is possible that following a bout of muscle-damaging
exercise the reduced exercise tolerance observed could be associated with a leftward shift
in these 31P metabolite-time profiles. Alternatively, an unchanged muscle metabolite
response would indicate that other, potentially central mechanisms may be responsible for
any decrements in endurance capacity. The purpose of this study was therefore to
investigate the effect of a well-defined bout of eccentric, muscle-damaging exercise
(Chapter 3) on changes in muscle metabolism during dynamic incremental knee extensor
exercise. We used 31P-MRS to test the hypothesis that exercise-induced muscle damage
(EIMD) alters the muscle metabolic response to dynamic exercise and thus limits exercise
tolerance in humans.

117
6.3 Methods
Subjects
Ten healthy, physically active male subjects (age, 22 ± 4 years; mass, 78.2 ± 8.8 kg; height,
1.79 ± 0.08 m) volunteered to participate in this study. All participants were asymptomatic
of illness and pre-existing injuries and had not performed any resistance training of the
lower limbs within the previous six months. Participants provided written informed
consent to participate in the study which was approved by the Institutional Ethics
Committee (See appendices B, C and D for exemplar participant information sheet,
participant consent form and ethical approval certificate).
Assessment of muscle damage
All indicators of muscle damage, perceived muscle soreness (using a 0-10 visual analogue
scale (VAS)), creatine kinase (CK) activity and isokinetic peak torque (30 deg.s-1), were
measured in the order listed, immediately before, and 24 and 48 h after performing the
eccentric, muscle-damaging exercise protocol. For further details of these procedures
please refer to Chapter 3.
Experimental procedures
Following the assessment of muscle damage, single -legged, knee-extension exercise tests
were completed at the same time of day ± 1 h for each participant, before and 48 h after
performing eccentric, muscle-damaging exercise. The dynamic knee-extensor exercise
tests were conducted in the prone position with the subjects positioned inside a whole body
MRI system. A 6-cm 31P transmit-receive surface coil was placed within the subject bed,
and the subject was asked to lie on it such that the coil was centred over the quadriceps

118
muscle of the leg to be exercised. Subjects were then secured to the ergometer bed with
Velcro straps at the thigh, buttocks, and lower back to minimise extraneous movement
during the protocol. The foot of the leg to be exercised was connected to a pulley system
that permitted a nonmagnetic weight to be lifted and lowered and work rate to be calculated
(Figure 6.1).
Exercise was performed at a rate of 40 repetitions/min with the subjects lifting and
lowering the mass over a distance of ~0.22 m in accordance with a visual cue projected
onto the front wall of the scanner room. The contraction phase of the knee extensors and
the 31P-MRS interrogation of the quadriceps occurred in unison. After a 2-min period of
rest, the subjects commenced knee-extension exercise against an initial basket load of 1 kg.
Thereafter, the basket load was increased by 0.5 kg every 30 s until the subjects were no
longer able to maintain the kicking frequency at 40 repetitions/min. The subjects received
strong verbal encouragement to continue for as long as possible while maintaining
appropriate form.
Eccentric, muscle-damaging exercise protocol
Participants completed 100 (Smith) squats, performed as 10 sets of 10 repetitions with the
load on the bar corresponding to ~70% of each participant’s body mass. Prior to
commencing, all participants were instructed in correct and safe lifting technique. The bar
was positioned on the participant’s shoulders and feet were positioned under the bar, with
the back straight and legs fully extended (knee = 180°). The descent phase involved
eccentric action of the knee extensors to lower the bar to a knee angle of just past 90°. The

Pulley system
Load basket
Subject lying in a prone
position within the core of
the whole body scanner.
The right foot is attached
to the pulley system.
119
lifting phase involved concentric action to return the bar to the starting position. For further
details of these procedures please refer to Chapter 3.
Figure 6.1 The MRS knee extensor ergometer showing pulley system and load basket.
Measurements
MRS measurements
MRS was performed in the Peninsula Magnetic Resonance Research Centre using a 1.5-T
superconducting magnetic resonance scanner (Philips Gyroscan Clinical Intera, Philips
Medical Systems, Best, Netherlands). Initially, fast-field echo images were acquired to

120
determine whether the muscle was positioned correctly relative to the coil. This was aided
by placing cod liver oil capsules, which yield high-intensity signal points within the image,
adjacent to the coil, allowing its orientation relative to the muscle volume under
examination to be assessed. A number of preacquisition steps were carried out to optimise
the signal from the muscle under investigation. Tuning and matching of the coil were then
performed, followed by an automatic shimming protocol undertaken within a volume that
defined the quadriceps muscle. The muscle volume from which signal originates is dictated
by the sensitive volume of the coil itself. This approximates to the physical size of the coil
and thus corresponds to a cylinder of 6cm diameter and 6cm deep adjacent to the coil.
Outside of this volume, muscle will still contribute to the signal but to an extent that drops
off rapidly as you move away from the sensitive region. To ensure that the examined
muscle was consistently at the same point relative to the coil during exercise, the subject
was visually queued via a display consisting of two vertical bars, one that moved at a
constant rate with a frequency of 0.67 Hz and one that monitored foot movements via a
sensor present within the pulley to which they were connected. Thus the subject
endeavoured to match the movements of these two bars. The work done by the subjects
was recorded via a nonmagnetic strain gauge present within the pulley mechanism. Before
exercise, during exercise, and during recovery, data were acquired every 1.5 s, with a
spectral width of 1,500 Hz and 1,000 data points. Phase cycling with eight phase cycles
was employed, leading to a spectra being acquired every 12 s. The subsequent spectra were
quantified via peak fitting, assuming prior knowledge, using the jMRUI (version 2)
software package and the AMARES fitting algorithm (Vanhamme et al., 1997; Naressi et
al., 2001).

121
Spectra were fitted assuming the presence of the following peaks: Pi, phosphodiester,
phosphocreatine (PCr), α-ATP (2 peaks, amplitude ratio 1:1), γ-ATP (2 peaks, amplitude
ratio 1:1), and β-ATP (3 peaks, amplitude ratio 1:2:1). In all cases, relative amplitudes were
corrected for partial saturation because of the short repetition time relative to the
longitudinal relaxation time constant T1. Absolute concentrations were determined by
calculating the size of peak areas relative to β-ATP which was set at 8.2 mM. The ratio of
Pi to PCr was determined from the respective Pi and PCr spectral areas as obtained during
the quantification procedure. Intracellular pH was calculated from the chemical shift of the
Pi spectral peak relative to the PCr (Moon and Richards, 1973). ADP concentrations were
calculated as described by Kemp et al., (2001) taking into account the pH dependency of
the binding of H+, K+ and Mg2+. To determine the intracellular threshold (IT) during
incremental exercise, piecewise linear regression was used. Briefly, different two-line
combinations were fitted to the [Pi]/[PCr]-work rate and pH-work rate relationships until
the lowest sum of squared residuals was found (Hogan et al., 1983; Marsh et al., 1991). The
point at which this particular two-line combination intersected was accepted as the IT.
Statistical analysis
Changes in the indicators of muscle damage (perceived muscle soreness, creatine kinase
activity and isokinetic peak torque) were analysed using a series of one-way repeated
measures ANOVAs. As the CK activity data were not normally distributed these values
were log-transformed prior to statistical analysis (Twist & Eston, 2005) (see appendix H).
Paired t-tests were used to determine significant differences in end exercise values
between the two conditions. Where data were not normally distributed Wilcoxon tests were
also run. Changes in the MRS measurements (Pi, PCr, Pi:PCr ratio and pH) at rest and

122
after 2, 4 and 6 min of incremental exercise were examined using separate two-way fully
repeated measure ANOVAs (condition x time). The assumption of sphericity was
evaluated using Mauchly’s test. Where sphericity was violated (P < 0.05), the Greenhouse-
Geisser (GG) correction factor was applied. All data were analysed using the statistical
software package SPSS for Windows (version 13) with statistical significance set at 0.05.
Values are means ± SD.
6.4 Results
Muscle damage
There were significant changes in all indicators of muscle damage following eccentric
exercise. Table 6.1 shows changes in muscle soreness, CK activity and isokinetic peak
torque before and after eccentric exercise. Muscle soreness increased 24 h after eccentric
exercise with the highest values reported at 48 h (F (2, 18) = 26.22, P < 0.05). Plasma CK
activity increased after eccentric exercise, with the highest values observed at 24 h (FGG (1.1,
9.9) = 15.02, P < 0.05).
Isokinetic peak torque (30 deg.s-1) decreased by 15% at 24 h and
remained 11% lower than baseline values at 48 h (F (2, 18) = 14.33, P < 0.05).

123
Table 6.1 Changes in indicators of muscle damage. Mean ± SD values and (range)
before and 24 h and 48 h after eccentric exercise.
Measured Variable before 24 h 48 h
Soreness (0-10 VAS)
0.5 ±
0.3
(0.1 –
1.1)
5.0 ±
2.0*
(1.8 –
8.2)
5.5 ± 3.2*
(1.6 – 9.7)
CK activity (U/L) 178 ±
61
(97 – 270)
798 ±
692*
(196 –
2481)
409 ± 264*
(213 – 1088)
Peak Torque (N.m)
30 deg.s
-1
310 ± 47
(227 –
366)
265 ±
66*
(113 –
340)
275 ± 77*
(115 - 361)
Soreness, visual analogue scale (VAS) 0–10. CK, creatine kinase.
* Significantly different from pre-eccentric exercise value (P < 0.05).
MRS measurements
As anticipated, time to exhaustion (519 ± 56 and 459 ± 63 s, pre and post muscle damage
respectively) and associated peak work rate values (29 ± 4 and 25 ± 4 W, pre and post
muscle damage respectively) attained during the incremental knee extensor exercise were
significantly reduced following muscle damage (t(9) = 4.85, P < 0.05 and t(9) = 5.21, P <
0.05, respectively). End exercise values are presented in Table 6.2. The data for end
exercise [Pi]:[PCr] and ADP were not normally distributed therefore Wilcoxon tests were
used to analyse these data. However results did not differ from t-test results therefore for
consistency the results of the paired t-tests are presented.
124
Table 6.2 Muscle metabolic responses at rest and during incremental exercise before
(Pre) and 48h after (Post) eccentric, muscle-damaging exercise. Values are means ± SD.
Measured
Variable Resting 2 min 4 min 6 min End
[PCr] (mM) †Pre
38.3 ± 1.2 35.0 ± 2.1 30.7 ± 3.1 24.3 ± 4.0 7.2 ± 1.7
Post
37.9 ± 1.4 34.1 ± 2.6 31.3 ± 3.0 25.5 ± 4.8 14.5 ± 2.1*
[Pi] (mM) †Pre
4.7 ± 0.8 5.6 ± 1.1 8.0 ±1.9 10.6 ± 3.0 19.7 ± 1.9
Post ‡
6.7 ± 1.7 7.5 ± 2.1 10.4 ± 4.0 14.8 ± 6.5 21.1 ± 2.6
[Pi]:[PCr] ratio†Pre
0.12 ±
0.02
0.16 ±
0.03
0.26 ±
0.05
0.45 ±
0.13
2.09 (1.74-14.4) ††
Post ‡
0.18 ±
0.05
0.22 ±
0.07
0.34 ±
0.15
0.62 ±
0.34
1.46 (0.85-2.29) ††*
pH
†
Pre 7.02 ±
0.03
7.06 ±
0.04
7.03 ±
0.04
6.96 ±
0.06
6.75 ± 0.04
Post
7.02 ±
0.03
7.07 ±
0.03
7.04 ±
0.05
6.99 ±
0.09
6.83 ± 0.04*
† Significant main effect for time (resting, 2, 4 and 6 min) (P < 0.05)
‡ Significant main effect for condition (Pre and Post) (P < 0.05)
* Significantly different from Pre-eccentric exercise (P < 0.05)
†† End exercise [Pi]:[PCr] ratio data were not normally distributed therefore values are
presented as median (interquartile range).
Table 6.3 Intracellular Threshold (IT) values before (Pre) and 48h after (Post) eccentric,
muscle-damaging exercise. Values are means ± SD.
Measured Variable Pre Post
Time @ IT (s)
326 ± 77 316 ± 65
[Pi]:[PCr] ratio @ IT
0.30 ± 0.14 0.31 ± 0.10
pH @ IT
7.07 ± 0.02 7.08 ± 0.02

125
End exercise pH and [PCr] values were higher (t(9) = -2.34, P < 0.05 and t(9) = -4.49, P <
0.05, respectively) and end exercise [Pi]:[PCr] values were lower (t(9) = 2.346, P < 0.05,)
following eccentric exercise. However, end exercise [Pi] and ADP were not significantly
different following eccentric exercise (t(9) = -0.496, P > 0.05 and t(9) = 1.82, P > 0.05,
respectively). The IT was not significantly altered by eccentric exercise (t(9) = 0.51, P >
0.05). The time, [Pi]:[PCr] and pH values when the IT occurred are presented in Table 6.3.
Prior to eccentric exercise, all ten participants completed a minimum of 7 min exhaustive
incremental exercise. However, 48 h after eccentric exercise the minimum time achieved
by all participants was reduced to 6 min. Thus, the first 6 min of incremental exercise were
analysed in order to examine changes in muscle metabolic responses during exercise.
45
40
35
30
25
20
15
10
5
0
0 60 120 180 240 300 360 420 480 540 600
Time (s)
Figure 6.2 [PCr] response of a representative participant, pre- and post-eccentric,
muscle damaging exercise. Vertical arrows indicate time to exhaustion in the two exercise
conditions. The solid line represents time to exhaustion pre-eccentric exercise; the dashed
line represents time to exhaustion post-eccentric exercise.
Pre-eccentric exercise
Post-eccentric
exercise
[PCr] (mM)
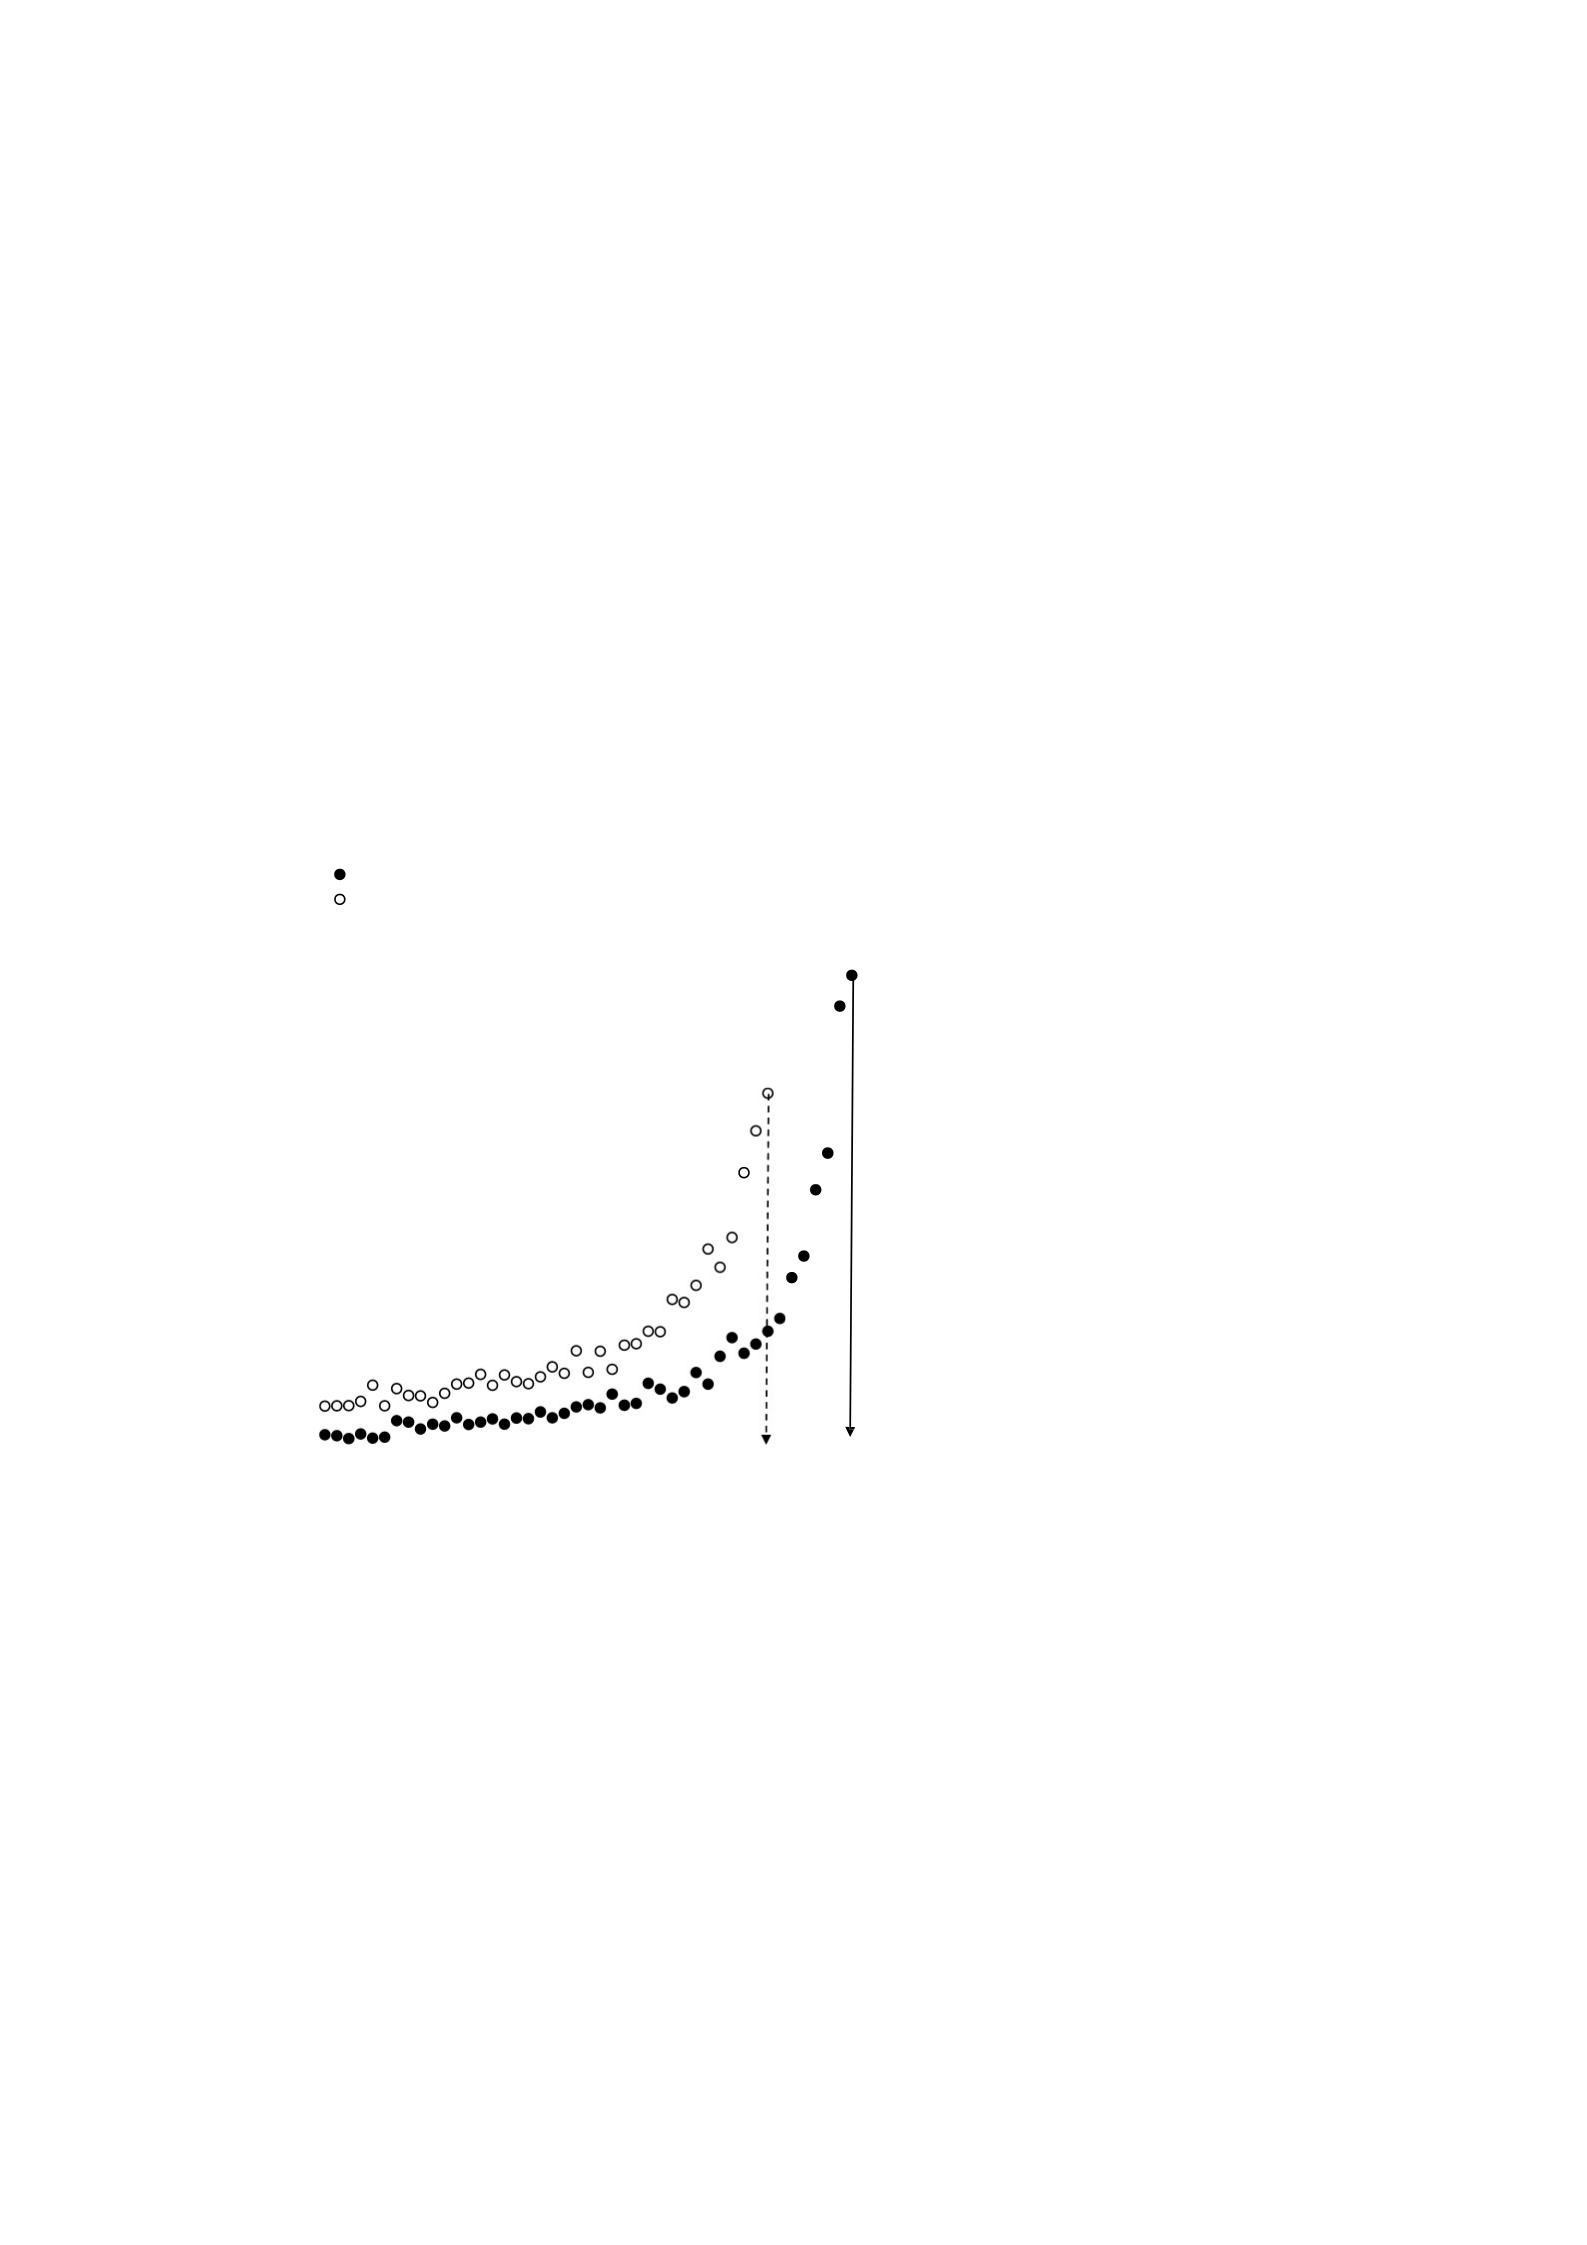
126
Muscle metabolic responses at rest and during incremental exercise are presented in Table
6.2 (see appendix I for graphical representation of these data). There was a significant
main effect for time for all muscle metabolic responses, with [PCr] and pH values
declining, and [Pi] and [Pi]:[PCr] values increasing as the incremental exercise progressed
(all P < 0.05). There was a significant main effect for condition for [Pi] (F(1,9) = 7.080, P <
0.05). Resting [Pi] values were significantly elevated and this mean difference was
maintained during the first 6 min of incremental exercise.
2.5
2
1.5
1
0.5
0
0 60 120
180
240
300
360
420
480
540
600
Time (s)
Figure 6.3 [Pi]:[PCr] response of a representative participant, pre- and post-eccentric,
muscle damaging exercise. Vertical arrows indicate time to exhaustion in the two exercise
conditions. The solid line represents time to exhaustion pre-eccentric exercise; the dashed
line represents time to exhaustion post-eccentric exercise.
Pre-eccentric exercise
Post-eccentric
exercise
[Pi]:[PCr]

127
As a direct consequence, [Pi]:[PCr] values were also elevated at rest and during the first 6
min of exercise (F(1,9) = 5.908, P < 0.05). In contrast, [PCr] and pH values were not
different between conditions at rest and during incremental exercise (both P > 0.05). There
were no significant interactions of condition and time for any muscle metabolic responses.
Changes in [PCr], [Pi]:[PCr] and pH are illustrated for a typical participant in Figures 6.2 -
6.4.
7.15
7.1
7.05
7
6.95
6.9
6.85
0 100 200 300 400 500 600
Time (s)
Figure 6.4
pH response of a representative participant, pre- and post-eccentric, muscle
damaging exercise. Vertical arrows indicate time to exhaustion in the two exercise
conditions. The solid line represents time to exhaustion pre-eccentric exercise; the dashed
line represents time to exhaustion post-eccentric exercise.
Pre-eccentric exercise
Post-eccentric
exercise
pH

128
6.5 Discussion
To our knowledge, this is the first study to investigate changes in muscle metabolism with
31P-MRS during incremental knee extensor exercise following an effective muscle-
damaging protocol. The principal original finding of this investigation was that the
reduction in time-to-exhaustion consequent to a bout of eccentric, muscle-damaging
exercise was not associated with an accelerated depletion of [PCr] or faster fall in pH.
Specifically, time-to-exhaustion was reduced by 12% following the muscle-damaging
exercise but the temporal changes in [PCr] and pH were similar in the two experimental
conditions such that end-exercise [PCr] and pH were significantly higher 48 h after the
muscle-damaging exercise (Figures 6.1 and 6.3). In contrast, the end-exercise [Pi] was not
significantly different between the pre- and post-EIMD conditions. These results indicate
that the reduced exercise tolerance following EIMD may be related either to the increased
[Pi] that was observed at rest and throughout incremental exercise, or to other unmeasured
peripheral or central factors. Importantly, however, the results allow us to discount a greater
rate of non-oxidative energy metabolism (as inferred from the changes in [PCr] and pH) as
important mediators of the reduced exercise tolerance following EIMD.
Our findings provide novel insights into changes in 31P metabolite responses to dynamic
exercise subsequent to muscle-damaging exercise. Previous research has reported
unaltered Pi:PCr ratio, pH and peak power during incremental exercise following a prior
bout of eccentric exercise (Rodenburg et al. 1995). However, these authors speculated that
the bench-stepping protocol employed to induce damage was not sufficiently strenuous to
elicit changes in exercise metabolism. Indeed, the lack of change in several markers of
muscle damage including maximum power output suggests that their eccentric exercise

129
protocol was ineffective (Rodenburg et al. 1995). Participants in the present study
completed a bout of eccentric, muscle-damaging exercise, comprising 100 squats with the
load on the bar set to 70% body mass (see chapter 3). This eccentric exercise protocol is
known to be effective in inducing damage (Byrne and Eston 2002a, 2002b). Indeed, in the
present study, there were changes in all measured symptoms of muscle damage. The
disruption of sarcomeres and myocyte membranes during unaccustomed eccentric exercise
leads to immediate and prolonged reductions in peak torque due to dysfunction of the
excitation-contraction (E-C) mechanism (Proske and Morgan 2001). The 11% reduction in
isokinetic peak torque observed at 48 h is consistent with previous studies which have
employed this eccentric exercise protocol in reflecting damage to the E-C mechanism
(Byrne and Eston 2002a, 2002b). Furthermore the significant increase in plasma CK
activity is indicative of increased membrane permeability. Impaired maximal force
production may, in part, account for the reduction in time to exhaustion and the associated
14% reduction in peak work rate values. The accelerated rate of fatigue experienced by our
participants is consistent with observations of impaired endurance performance brought
about by the effects of eccentric exercise (Asp et al. 1998; Marcora and Bosio 2007; Twist
and Eston 2009).
Peripheral fatigue factors originating from within the damaged muscle tissue have been
implicated in the reduction in endurance capacity associated with exercise-induced muscle
damage. Specifically, reports of increased blood lactate (Asp et al., 1998; Braun & Dutto,
2003; Chen et al., 2007) and increased utilisation of glycogen stores (Asp et al., 1998)
following eccentric exercise have been attributed to a putative shift towards an increased
reliance on anaerobic energy production leading to impaired endurance performance (Asp

130
et al., 1998; Braun & Dutto, 2003; Chen et al., 2007). However, in the present study, the
PCr response for a given work rate was not significantly altered, although the performance
of incremental knee extensor exercise was impaired.
It is recognised that muscle PCr and
V˙ O2 demonstrate similar kinetic profiles during transitions to higher exercise intensities
(Barstow et al., 1994; Mahler, 1985; Marsh et al., 1993), indicating that the rate of
oxidative phosphorylation is closely linked to PCr hydrolysis (Mahler, 1985, Meyer, 1988).
Thus our observation of an unchanged PCr profile during incremental exercise is consistent
with reports of unchanged
V˙ O2
kinetics following eccentric exercise (Schneider et al.,
2007). Collectively these data indicate that exercise-induced muscle damage does not
compromise oxidative function during dynamic exercise. The reduction in time to fatigue
resulted in significant alterations in end exercise [PCr] values. Prior to the bout of muscle-
damaging exercise the mean depletion of the PCr pool was over 80% at the end of the
incremental exercise, with several subjects almost completely depleting their muscle PCr.
However 48 h after the muscle-damage was induced, participants reached exhaustion
sooner with a mean depletion of the PCr pool of approximately 62%. Thus end-exercise
[PCr] was higher when incremental exercise was performed in the muscle-damaged
condition.
Similarly, intracellular pH demonstrated an unchanged rate of fall during incremental
exercise after muscle-damage was induced. There was no significant difference in the pH
values for a given work rate at 48 h although end exercise pH was higher due to the shorter
time to exhaustion. Furthermore, the unchanged [PCr] and pH responses to incremental
exercise resulted in there being no significant difference in the IT values following
eccentric exercise. Low [PCr] and pH have been implicated in the fatigue process

131
(Westerblad and Allen 2003; Wilson et al. 1988). However, on the evidence of our
observations these effects do not appear to be associated with the reduction in exercise
tolerance that accompanies exercise-induced muscle damage.
At rest, increases in [Pi], resulted in a 50% increase in the resting [Pi]:[PCr] ratio 48 h after
eccentric exercise. These findings are consistent with those of several previous studies
using 31P-MRS in reporting increases in resting [Pi]:[PCr] following eccentric exercise
(McCully 1992, Rodenburg et al., 1995; Lund et al., 1998a, 1998b). Elevated resting [Pi]
such as observed herein and elsewhere (McCully 1992, Rodenburg et al., 1995; Lund et al.,
1998a, 1998b) may be interpreted as an increase in muscle metabolism. The repair and
remodelling of tissue damaged via eccentric exercise such as that reported by Yu et al.
(2002) and Yu and Thornell (2002) could lead to an increase in resting muscle metabolism.
Furthermore, depleted resting muscle glycogen content following eccentric exercise,
particularly the content of the preferentially damaged type II fibres, has been attributed to
increased resting muscle glycogen utilisation (Asp et al., 1998). An alternative explanation
for the increase in [Pi]:[PCr] which, importantly, results from increased [Pi] but not
decreased [PCr], may be linked to the breakdown of muscle tissue consequent to eccentric
exercise. Disturbances in intracellular Ca2+ following eccentric exercise have been reported
with concomitant activation of calcium-activated proteolytic pathways (Belcastro, 1993;
Belcastro et al. 1998). Thus the observed increase in resting [Pi] may not be due to
increases in muscle metabolism but to the degradation of muscle proteins.
Increases in resting [Pi] and [Pi]:[PCr] following a period of cast immobilisation have been
implicated in the loss of muscular strength resultant to the period of disuse (Pathare et al.,

132
2005, 2008). Similarly, increases in the resting [Pi]:[PCr] ratio of patients with postpolio
residual paralysis, a condition which is characterised by decreased endurance capacity and
muscular weakness, is related to the severity of paralysis (Sharma et al., 2007). Increases
in intracellular [Pi] can inhibit force production via direct action on cross-bridge formation
or on sites in the excitation-contraction pathway and may play a key role in the
development of muscle fatigue (Westerblad et al., 2002). Thus the reduction in peak torque
and exercise tolerance observed in the present study following muscle damage, may be
related to the increased [Pi] and [Pi]:[PCr] which was observed not only at rest but also
during incremental exercise. The novel observation that the significant increases in resting
[Pi] and [Pi]:[PCr] at 48 h were maintained during the dynamic exercise test, is of particular
interest. The rate of increase in [Pi] during incremental exercise was not altered as a result
of the muscle damage. However the premature termination of the test at 48 h resulted in
there being no significant difference in end exercise [Pi] values. It might be tempting to
speculate that the limit to exercise tolerance was moderated by [Pi]. However wide inter-
subject variability was observed with the [Pi] values, thus we cannot reliably conclude that
[Pi] is indeed a limiting factor. Rather that end exercise [Pi] most likely makes an important
contribution to the reduced time to exhaustion experienced following muscle damaging
exercise.
Central fatigue factors including the production of inflammatory cytokines may be involved
in the reduced time to exhaustion following eccentric exercise observed herein. Carmichael
et al. (2005) have reported increases in brain IL-1β in areas responsible for movement,
motivation, perception of effort and pain, which have been associated with decreases in
treadmill runs to fatigue in mice. In human subjects, it has been proposed that the increased

133
sense of effort reported during dynamic exercise mediates time trial performance following
eccentric exercise (Marcora & Bosio 2007; Twist & Eston 2009) The duration of an
individual’s incremental exercise to ‘volitional exhaustion’ is regulated by a complex
interaction of central and peripheral fatigue factors. However, the decision to terminate
exercise is ultimately a conscious behavior based on the perception of alterations in sub-
conscious homeostatic control systems (St Clair Gibson et al., 2003). It is beyond the
scope of this study to determine whether central or peripheral factors make the greater
contribution to the accelerated fatigue development experienced with EIMD.
6.6 Conclusion
In conclusion, the results of this study suggest that the reduced exercise tolerance following
EIMD cannot be attributed to a greater rate of non-oxidative energy metabolism (as
inferred from the changes in [PCr] and pH). Although we cannot exclude an important role
for centrally-mediated fatigue, our results indicate that increases in resting [Pi], that are
maintained during exercise, may be a contributory factor to the reduced exercise tolerance
that is observed following EIMD.

The contents of this chapter form the basis of the following publication /presentation:
Publication
Davies RC, Eston RG, Poole DC, Rowlands AV, Dimenna F, Wilkerson DP, Twist C,
and Jones AM. The effect of eccentric exercise-induced muscle damage on the
dynamics of muscle oxygenation and pulmonary oxygen uptake. J Appl Physiol
(August 14, 2008). doi:10.1152/japplphysiol.90743.2008
Presentation
Davies R, Eston R, Poole D, Rowlands A, Dimenna F, Wilkerson D, Twist C, and
Jones A. The influence of exercise-induced muscle damage on pulmonary oxygen
uptake and muscle deoxygenation kinetics during high intensity exercise. 13th Annual
Congress of the European Congress of Sports Sciences, Book of Abstracts, edited by
Cabri J, Alves F, Araujo D, Barreiros J and Veloso A, Estoril, 2008, p630.
134
CHAPTER 7
THE EFFECT OF ECCENTRIC EXERCISE-INDUCED MUSCLE
DAMAGE ON THE DYNAMICS OF MUSCLE OXYGENATION AND
PULMONARY OXYGEN UPTAKE

135
7.1 Abstract
Unaccustomed eccentric exercise has a profound impact on muscle structure and function.
However, it is not known whether associated microvascular dysfunction disrupts the
matching of
O2 delivery ( Q˙ O2 ) to O2 utilisation ( V˙ O2 ). Near infra-red spectroscopy
(NIRS) was used to test the hypothesis that eccentric exercise-induced muscle damage
would
elevate
the
muscle Q˙ O2 : V˙ O2 ratio
during
severe
intensity exercise
whilst
preserving the speed of the V˙ O2 kinetics at exercise onset. Nine physically active men
completed ‘step’ tests to severe-intensity exercise from an unloaded baseline on a cycle
ergometer before and 48 h after eccentric exercise (100 squats with a load corresponding to
70%
of
body mass).
NIRS
and
breath-by-breath
pulmonary V˙ O2 were measured
continuously during the exercise tests and subsequently modelled using standard non-linear
regression
techniques. There
were
no
changes
in
phase
II
pulmonary V˙ O2 kinetics
following the onset of exercise (time constant, pre: 25 ± 4; post: 24 ± 2 s; amplitude, pre:
2.36 ± 0.23; post: 2.37 ± 0.23 L/min; all P>0.05). However, the primary (pre: 14 ± 3; post:
19 ± 3 s) and overall (pre: 16 ± 4; post: 21 ± 4 s) mean response time of the [HHb] response
was significantly slower following eccentric exercise (P<0.05). The slower [HHb] kinetics
observed following eccentric exercise is consistent with an increased
Q˙ O2 : V˙ O2 ratio
during transitions to severe-intensity exercise. We propose that unchanged primary phase
V˙ O2 kinetics are associated with an elevated Q˙ O2 : V˙ O2 ratio that preserves blood-
myocyte O2 flux.

136
7.2 Introduction
Unaccustomed eccentric exercise has a profound impact on muscle structure and function.
Following such exercise, myocytes demonstrate ultra-structural changes including
sarcomere disruption described as ‘popping’ (Morgan, 1990), ‘Z-band streaming’ (Fridén &
Lieber, 2001; Stupka et al., 2001) or ‘smearing’(Kano et al., 2005), and damage to t-
tubules, sarcoplasmic reticulum and sarcolemma (Fridén & Lieber, 2001 ). This disruption
leads to increased influx of extracellular Ca2+ into the sarcoplasm, leading to enhanced
proteolytic enzyme activity (Proske et al., 2004) and an accompanying inflammatory
response (Fielding et al., 1993). In addition, intramyocyte contents such as creatine kinase
and myoglobin are released into the bloodstream (Warren et al., 1999). These degenerative
changes are associated with delayed onset muscle soreness (DOMS) and a reduction in
maximal force generating capacity (Byrne et al., 2004; Clarkson, 1992; Cleak & Eston,
1992).
As myocyte degeneration is known to lead to decrements in maximal force production, any
associated damage to the microcirculation could potentially have an adverse affect on sub-
maximal locomotory activity such as running or cycling. Activities that require repetitive
low-force contractions rely on effective vascular function that ensures an adequate blood
and O2 supply to muscle. Accordingly, Kano et al. (2005) have reported substantial
microvascular dysfunction in rat spinotrapezius muscle following unaccustomed eccentric
exercise (downhill running). Specifically, these authors reported an increase in the
proportion of capillaries that did not support red blood cell (RBC) flux and an increase in
mean capillary diameter in resting muscle. Furthermore, an accelerated fall in
microvascular oxygen pressure was observed at the onset of electrically stimulated

137
contractions. Microcirculatory dysfunction such as this could conceivably lead to impaired
delivery and distribution of O2 within the capillary bed. Similarly, the matching of O2
delivery ( Q˙ O2 ) and O2 utilisation ( V˙ O2 ) at the onset of exercise might be
disturbed, thereby compromising blood-muscle O2 flux and, if sufficiently severe, slow the
kinetic adaptation of V˙ O2 at exercise onset (Kano et al., 2005). Although the compelling
weight of
evidence supports the premise that V˙ O2 kinetics in healthy individuals are not limited by
O2 delivery, per se, in disease conditions such as chronic heart failure (Richardson et al.,
2003) and Type II diabetes (Padilla et al., 2006) where vascular function and capillary
haemodynamics are impaired, V˙ O2 kinetics are slowed (Poole et al., 2005). It is possible
that microcirculatory dysfunction brought about by previous eccentric exercise could result
in the V˙ O2 kinetics of healthy individuals becoming slower due to a muscle O2 delivery
limitation. That is, the muscle damage could cause individuals to cross the so-called
‘tipping point’ beyond which reductions in muscle O2 availability begin to measurably
lengthen the time constant describing the phase II V˙ O2 response (Poole et al., 2008).
Near infrared spectroscopy (NIRS) facilitates the assessment of muscle (haemoglobin +
myoglobin) oxygenation and can thus be utilised to determine the dynamic balance between
Q˙ O2 and V˙ O2 following the onset of exercise. In particular, the deoxyhaemoglobin
(HHb) concentration ([HHb]) NIRS signal can be used to non-invasively estimate O2
extraction in the skeletal muscle microcirculation. Thus, the NIRS-derived [HHb] signal
would be expected to demonstrate a slower kinetic response at the onset of exercise if, as

138
anticipated, eccentric exercise does compromise blood-muscle O2 flux.

139
One recent investigation by Schneider et al. (2007) reported no change in V˙ O2 kinetics at
the onset of heavy intensity exercise 48 and 72 h following bench-stepping exercise
designed to incur damage. An explanation for this apparent paradox, i.e. normal
V˙ O2
kinetics in the face of severe muscle damage and impaired microvascular haemodynamics,
may be found in the work of Laaksonen et al. (2006) who reported that muscle damage
increased muscle blood flow during exercise. If microvascular function and therefore the
ability to match Q˙ O2 : V˙ O2
effectively is compromised following eccentrically exercised
muscle, it is possible that an elevation in the Q˙ O2 : V˙ O2 ratio would serve to raise
capillary O2 pressures and restore blood-tissue O2 flux in the face of capillary haemodynamic
derangements. Accordingly, the present investigation utilised NIRS to test the novel
hypothesis that eccentric exercise-induced muscle damage would elevate the muscle Q˙
O2 :
V˙ O2 ratio (as indicated by alterations in the [HHb] kinetics) during severe intensity
exercise and thus preserve the speed of the V˙ O2 kinetics at exercise onset.
7.3 Methods
Participants
Nine healthy men (mean ± S.D. age 22.7 ± 2.8 years; height 1.83 ± 0.06 m; mass 76.7 ± 7.0
kg), asymptomatic of illness and pre-existing injury, volunteered to participate in the study.
All were physically active but were not highly trained and had not undertaken any
resistance training of the lower limbs for at least six months prior to assessment.
Participants provided written informed consent to participate in the research which was
approved by the Ethics Committee of the School of Sport and Health Sciences at the

140
University of Exeter and conformed to the Declaration of Helsinki (See appendices B, C
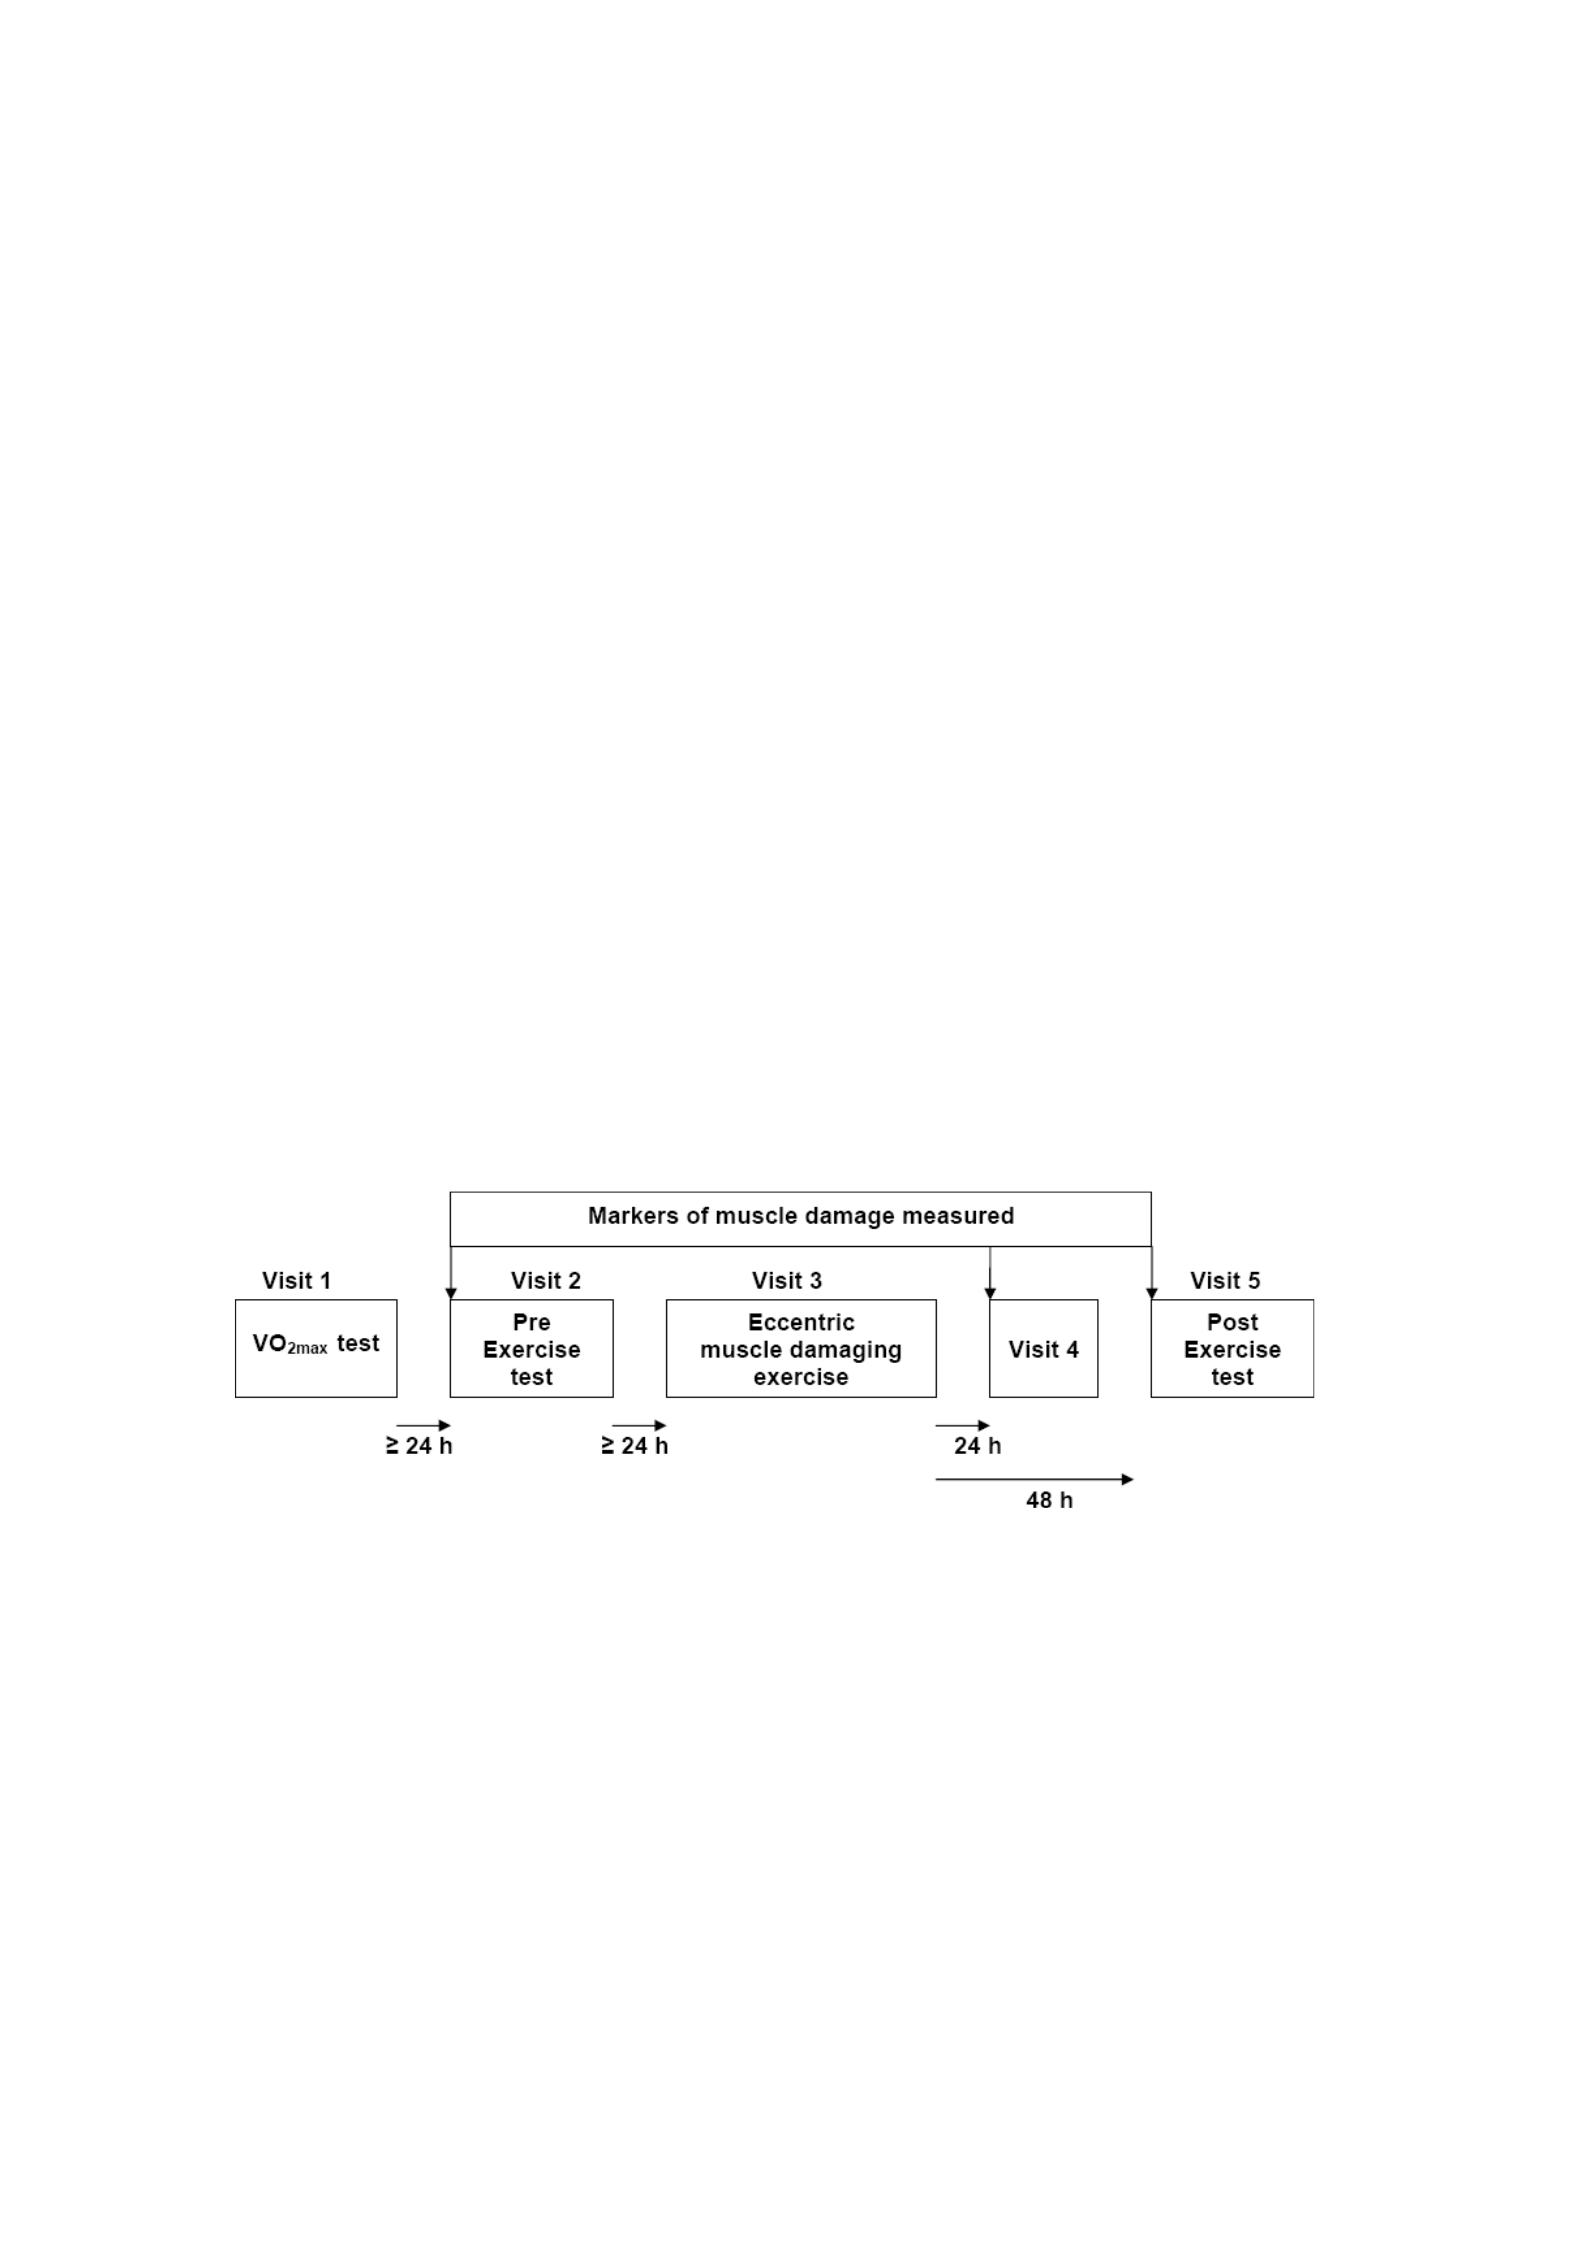
141
and D for exemplar participant information sheet, participant consent form and ethical
approval certificate). The participants were requested not to take any anti-inflammatory
drugs for the duration of the study and to refrain from heavy exercise for 24 h prior to each
visit.
Procedures
All testing was performed on an electronically-braked cycle ergometer (Lode Excalibur
Sport, Groningen, Netherlands). The participants were instructed to report to the laboratory
at the same time of day (± 1 h) on five separate occasions within a period of 2-3 weeks
(Figure 7.1). On the first visit to the laboratory seat height and handlebar positions were
individually adjusted for comfort and the adjustments were recorded and replicated in
subsequent tests. The height and mass (SECA, UK) of each participant was also recorded.
Figure 7.1 Schematic overview of experimental procedures. V˙ O2 max,
Maximal oxygen uptake.

142
Participants then completed an incremental exercise test to volitional exhaustion to
determine maximal oxygen uptake ( V˙ O2 max) and gas exchange threshold (GET) and to
establish future work intensities. This entailed cycling at a self-selected pedal rate (between
70 and 90 rpm) for 4 minutes of baseline cycling at 0 W. The work rate was then increased
in a ramp fashion by 1 W every 2 s (i.e. 30 W.min−1) until the subject was unable to
continue. The
V˙ O2 max was defined as the highest 30-s mean value recorded before the
subject’s volitional termination of the test. The GET was determined independently by two
experienced reviewers using the V-slope method (Beaver et al., 1986). The work rate that
required 70% of the difference () between the GET and V˙ O2 peak (severe exercise) was
calculated, with account taken of the mean response time of the V˙ O2 adaptation to ramp
exercise (approximately 2/3 of the ramp rate i.e. minus 20 W) (Whipp, 1984). On the
second and fifth visits, pre and 48 h after the eccentric muscle damaging exercise
respectively, participants cycled at a self-selected pedal rate (between 70 and 90 rpm) for 4
minutes at 0 W, after which a warm-up phase at moderate intensity (~ 80% GET) was
applied for a further 6 minutes. After 2 minutes of passive rest, the subjects pedalled for 4
minutes of baseline cycling at 0 W after which the severe work rate was abruptly applied
for 6 minutes. This test was repeated after a rest period of 2 hours. In the second test, the
severe exercise bout was continued until the subject volitionally terminated the test at
exhaustion.
Eccentric exercise
In order to provoke muscle damage, participants performed 100 (Smith) squats as 10 sets of
10 repetitions. The load on the bar was calculated to correspond to 70% of each

143
participant’s body mass. For further details of these procedures please refer to Chapter 3.

144
Measurements
Markers of muscle damage
Markers of muscle damage (muscle soreness and isokinetic peak torque) were measured
immediately before and then 30 minutes and 48 hours after eccentric exercise. In addition
plasma creatine kinase (CK) activity was assessed immediately before and then 30 minutes,
24 and 48 hours after eccentric exercise. Due to availability at 24 h, only 8 participants
were measured for CK activity.
Assessment of muscle damage
All indicators of muscle damage, perceived muscle soreness (using a 0-10 visual analogue
scale (VAS)), creatine kinase (CK) activity and isokinetic peak torque (30 deg.s-1), were
measured in the order listed, immediately before, and 24 and 48 h after performing the
eccentric, muscle-damaging exercise protocol. For further details of these procedures
please refer to Chapter 3.
Exercise test measures
Pulmonary gas exchange and ventilation were measured breath-by-breath throughout all
tests with participants wearing a nose clip and breathing through a low-dead-space, low-
resistance mouthpiece via an online gas analysis system (Cortex MetaMax 3B, Biophysik,
Leipzig, Germany). The system was calibrated prior to every test in accordance with
manufacturer’s guidelines against known concentrations of cylinder gases (5% oxygen,
15% carbon dioxide) and a 3 l calibration syringe (Hans Rudolph, Kansas City, MO). The

145
V˙ O2data gathered from the pre- and post- exercise tests were subsequently modelled to
provide estimates of the V˙ O2 kinetic parameters (see Modelling of V˙O2 and [HHb] data).
Heart rate (HR), blood lactate concentration ([La]) and Ratings of Perceived Exertion
(RPE) (Borg, 1998) were recorded at 2 min, 4 min and at the end of exercise. HR and [La]
measures were also recorded during baseline cycling. HR was monitored using a wireless
chest strap telemetry system (Polar Electro T31, Kempele, Finland) and measured
continuously via a link to the Cortex gas analysis system. Fingertip blood samples were
collected and analysed for [La] using an YSI 2300 STAT plus analyzer (Yellow Springs,
Ohio, USA). Participants were familiarized with Borg’s 6-20 RPE Scale and provided with
standardised instructions on how to employ the scale (Borg, 1998). Participants were
encouraged to focus on their overall perception of exertion when reporting their RPE.
Near-infrared spectroscopy (NIRS)
Oxygenation profiles of the right vastus lateralis muscle were recorded in all exercise tests
using a continuous wave near-infrared spectrometer (NIRS) (Hamamatsu NIRO 300,
Hamamatsu Photonics KK, Japan) (Figure 7.2). The system monitored concentration
changes in oxyhaemoglobin (HbO2) and deoxyhaemoglobin (HHb) which were calculated
from the light attenuation change by utilising the modified Beer-Lambert law. The HHb
concentration ([HHb]) signal obtained from the NIRS was regarded as being relatively
insensitive to blood volume changes during exercise and thus reflected the balance between
the delivery and utilisation of oxygen (Ferrari et al., 1997).

146
Figure 7.2 Measurement principle and probe structure of the NIRO 300 (Hamamatsu,
Hamamatsu Photonics KK, Japan)
Pulsed light was emitted at 1 s intervals from the emission probe at four different
wavelengths (775, 810, 850 and 910nm) and was detected, as a function of distance, using a
three segment photodiode detection probe that received NIRS signals at 2 Hz. The probes
were housed in the black silicone holder provided. The inter-optode spacing between
emitter and receiver was 4 cm, and the penetration depth was approximately half of the
distance between the emitter and the receiver, i.e. 2 cm. Prior to placement on the right
vastus lateralis, the site was shaved and cleaned using an alcohol swab. The NIRO300
system was then calibrated and the probe holder secured by means of a double-sided
adhesive sheet ~12 cm above the lateral epicondyle of the right leg, with the location
marked using an indelible marker pen to enable reproduction of the probe positions in
subsequent tests (48 h). The thigh with attached probe holder was then wrapped in a dark-
coloured, elastic bandage to further secure the probes and to eliminate ambient light that
might contaminate the NIRS signal (Figure 7.3)

147
Figure 7.3. Attachment of the NIRS probes. The NIRS probe holder is secured by
means of a double-sided adhesive (a). The thigh with attached NIRS probe holder is
wrapped in an elastic bandage (b).
The NIRS data gathered represented relative concentration changes in the haemoglobin
chromophores and were, therefore, not representative of absolute tissue O2 values. As
[HHb] was measured as a change from baseline values the probe gain was zero set prior to
testing with the subject at rest in a seated position. Differences in the thickness of the
overlying adipose tissue may influence the amplitude of the NIRS signal. However, the
same subjects were employed pre- and post eccentric exercise and the probe positions were
rigorously maintained for each subject in each test, thus no correction for inter-site
adiposity was necessary. Following exercise testing the data were downloaded and the
resulting text files stored for subsequent analysis.
(a) (b)

148
Modelling of V˙O2 and [HHb] data
The breath-by-breath data from each exercise test were filtered manually to remove
outlying breaths, defined as breaths ± 3 SD from the adjacent five breaths. The data for
each individual were then interpolated to provide 1 s values and the two data sets from each
of the pre- and post- exercise tests were time-aligned and averaged. The first 20 s of data
after the onset of exercise (the Phase I response) were deleted and a biexponential model
was used to analyze the V˙ O2 responses to severe exercise, as described by the following
equation:
V˙ O2 (t) = V˙ O2 baseline
+ Ap[1 – e
-
(t
-
Tdp)/
τp
] (phase 2 / primary component)
+ As[1 – e
-
(t
–
Tds)/
τs
] (phase 3 / slow component)
where t is time;
V˙ O2 baseline is baseline
V˙ O2 ; Ap and As are the primary and slow
component amplitude, respectively; Tdp and Tds are the primary and slow component time
delays, respectively; and τp and τs are the time constants of the primary and slow
components respectively.
The parameters
of the
model
were determined
by
using
a
nonlinear least squares algorithm. In the equations above, V˙ O2 (t) represents the absolute
V˙ O2
at a given time t, and V˙ O2 baseline represents the average V˙ O2
through the baseline
cycling period. Because the time to exhaustion was not identical in the first and second
bouts of severe exercise, we fitted the data 1) to the end of exercise in both bouts and 2) to
the same point in time (given by the time to exhaustion in the shortest bout). The primary

149
component “gain” (i.e., Ap/∆WR) was calculated from the projected asymptotic V˙ O2 . In
addition, the “actual” gain attained at the end of exercise was calculated.
To provide information on the effect of eccentric muscle-damaging exercise on the
dynamics of muscle oxygenation, we also modelled the ∆[HHb] response to severe
exercise. The NIRS-derived [HHb] data were time-aligned and averaged to provide a single
response for each subject pre- and post- eccentric exercise. The time delay before an
increase in [HHb] after exercise onset was determined as the first point greater than one
standard deviation above the mean of the baseline (DeLorey et al., 2003). [HHb] data were
then fitted with a bi-exponential model similar to that described by the equation above, with
the exception that the fitting window started at the onset of exercise (i.e., at time 0).
Subsequently, [HHb] data were fitted with a mono-exponential model from the onset of
exercise to the time point representing the interface of the primary and slow component to
determine the rate of adaptation of muscle deoxygenation during the primary phase
(MRT1). In addition, the [HHb] dynamics for the entire response were modelled with a
similar mono-exponential function (MRTt).
Statistical analysis
Changes in the markers of muscle damage (peak torque, soreness and CK activity) were
analysed using a series of one-way repeated measures (RM) ANOVA. All data were
checked for assumptions of normality. As the CK activity data were found not to be
normally distributed, the values were log-transformed prior to statistical analysis (Twist &
Eston, 2005) (see appendix H).

150
Following transformation CK activity data were normally distributed. Changes in HR,
RPE, [La] and ventilation were analysed using separate 2-way RM ANOVAs (test x time).
Assumptions of sphericity were evaluated using Mauchly’s test. Where sphericity was
violated (P< 0.05) the Greenhouse-Geisser (GG) correction factor was applied. Post-hoc
Tukey tests modified for repeated measures (Stevens, 2002) were run to determine where
significant
differences
occurred.
Paired
t-tests
were
used
to
determine
significant
differences in time-to-exhaustion and the V˙
O2
and [HHb] kinetic responses to severe
intensity exercise before and after eccentric exercise. All data were analysed using the
statistical software package SPSS for Windows (version 13). Statistical significance was set
at 0.05.
7.4 Results
Markers of muscle damage
The eccentric exercise was effective in provoking significant changes in all markers of
muscle damage. Table 7.1 shows changes in isokinetic peak torque, perceived muscle
soreness and plasma CK activity before and at 24 h and 48 h post eccentric exercise.
151
Table 7.1 Changes in markers of muscle damage. Mean ± SD values before (pre)
and at 24 h and 48 h after eccentric exercise.
Measured variable pre 24 h post 48 h post
Peak Torque (N.m) 30 deg.s-1 287 ± 39 227 ± 44* 228 ± 60*
Soreness 0.6 ± 0.5 6.4 ± 1.8* 7.1 ± 1.5*
CK activity (U/L) 172 ± 123 740 ± 666* 373 ± 208
Values are means ± SD before (pre) and 24 h and 48 h after eccentric exercise (post).
Soreness, visual
analogue scale 0-10. CK, creatine kinase. *significantly different (P < 0.05) from pre value
Isokinetic peak torque (30 deg.s-1) decreased by 21% at 24 h post-eccentric exercise and
remained depressed at 48 h (F (2,16) = 21.85 p < 0.001). Significant soreness was reported
24 h after eccentric exercise with the highest values at 48 h (F (2,14) = 80.50 p < 0.001).
Plasma CK activity increased after eccentric exercise, with the highest activity observed at
24 h (F (2,16) = 17.15 p < 0.001). Changes in markers of muscle damage were detected in all
subjects, although considerable inter-subject variability was observed. Peak decrements in
isokinetic peak torque (30 deg.s-1) ranged from 12 - 44%, and peak increases in soreness
and plasma CK activity ranged from 53 - 95% and 146 - 1176%, respectively.
Response to severe intensity exercise
Table 7.2 shows the V˙ O2 responses to severe intensity exercise. There were no changes in
the phase II V˙ O2 kinetics following eccentric exercise, nor was there a change in the slow
component time delay (TD) (P > 0.05). However the amplitude of the slow component was
significantly reduced (t (8) = 3.84, P < 0.05) and the overall mean response time (MRT) was
significantly faster (t (8) = 4.01, P < 0.05) following eccentric exercise. A significantly
shorter time to exhaustion was observed in the 2nd bout of severe intensity exercise (pre:

152
7:24 min:s (± 2:41) post 6:14 min:s (± 2:46)) (t (8) = 2.58, P < 0.05). The V˙ O2 response of
a representative subject is illustrated in Figure 7.4.
Table 7.2
Pulmonary O2 uptake responses to severe intensity exercise before and after
eccentric muscle damaging exercise.
Pre 48 h post
Primary component
TDp (s) 12 ± 4 12 ± 2
p (s) 25 ± 4 24 ± 3
Ap V˙ O2 (L·min-1)2.36 ± 0.23 2.37 ± 0.23
Gain (mL·min-1·W-1)9.02 ± 0.45 9.04 ± 0.52
Slow component
TD2 (s) 102 ± 19 107 ± 29
A2ref V˙ O2 (L·min-1)0.63 ± 0.33 0.37 ± 0.17*
A2end V˙ O2 (L·min-1)0.67 ± 0.33 0.38 ± 0.17*
Overall response
MRT
ref
61 ± 15 51 ± 9*
MRT
end
64 ± 15 51 ± 9*
Peak V˙ O2 (L·min-1)3.89 ± 0.44 3.70 ± 0.36
Values are means ± SD. TDp, p. Ap and gain are the time delay, time constant, amplitude and increase in
V˙ O2 per unit increase in work rate for phase II kinetics respectively. TD2, A2ref and A2end are the time delay,
amplitude to 6 mins and amplitude to end of exercise for the slow component, respectively. MRTend and
MRTref are the mean response times fitted to the end of exercise in both bouts and to the same point in time
(given by the time to exhaustion in the shortest bout), respectively. Peak V˙ O2 tended to be lower post-
eccentric exercise but the difference was not statistically significant. Significant difference (P < 0.05) from
pre value.
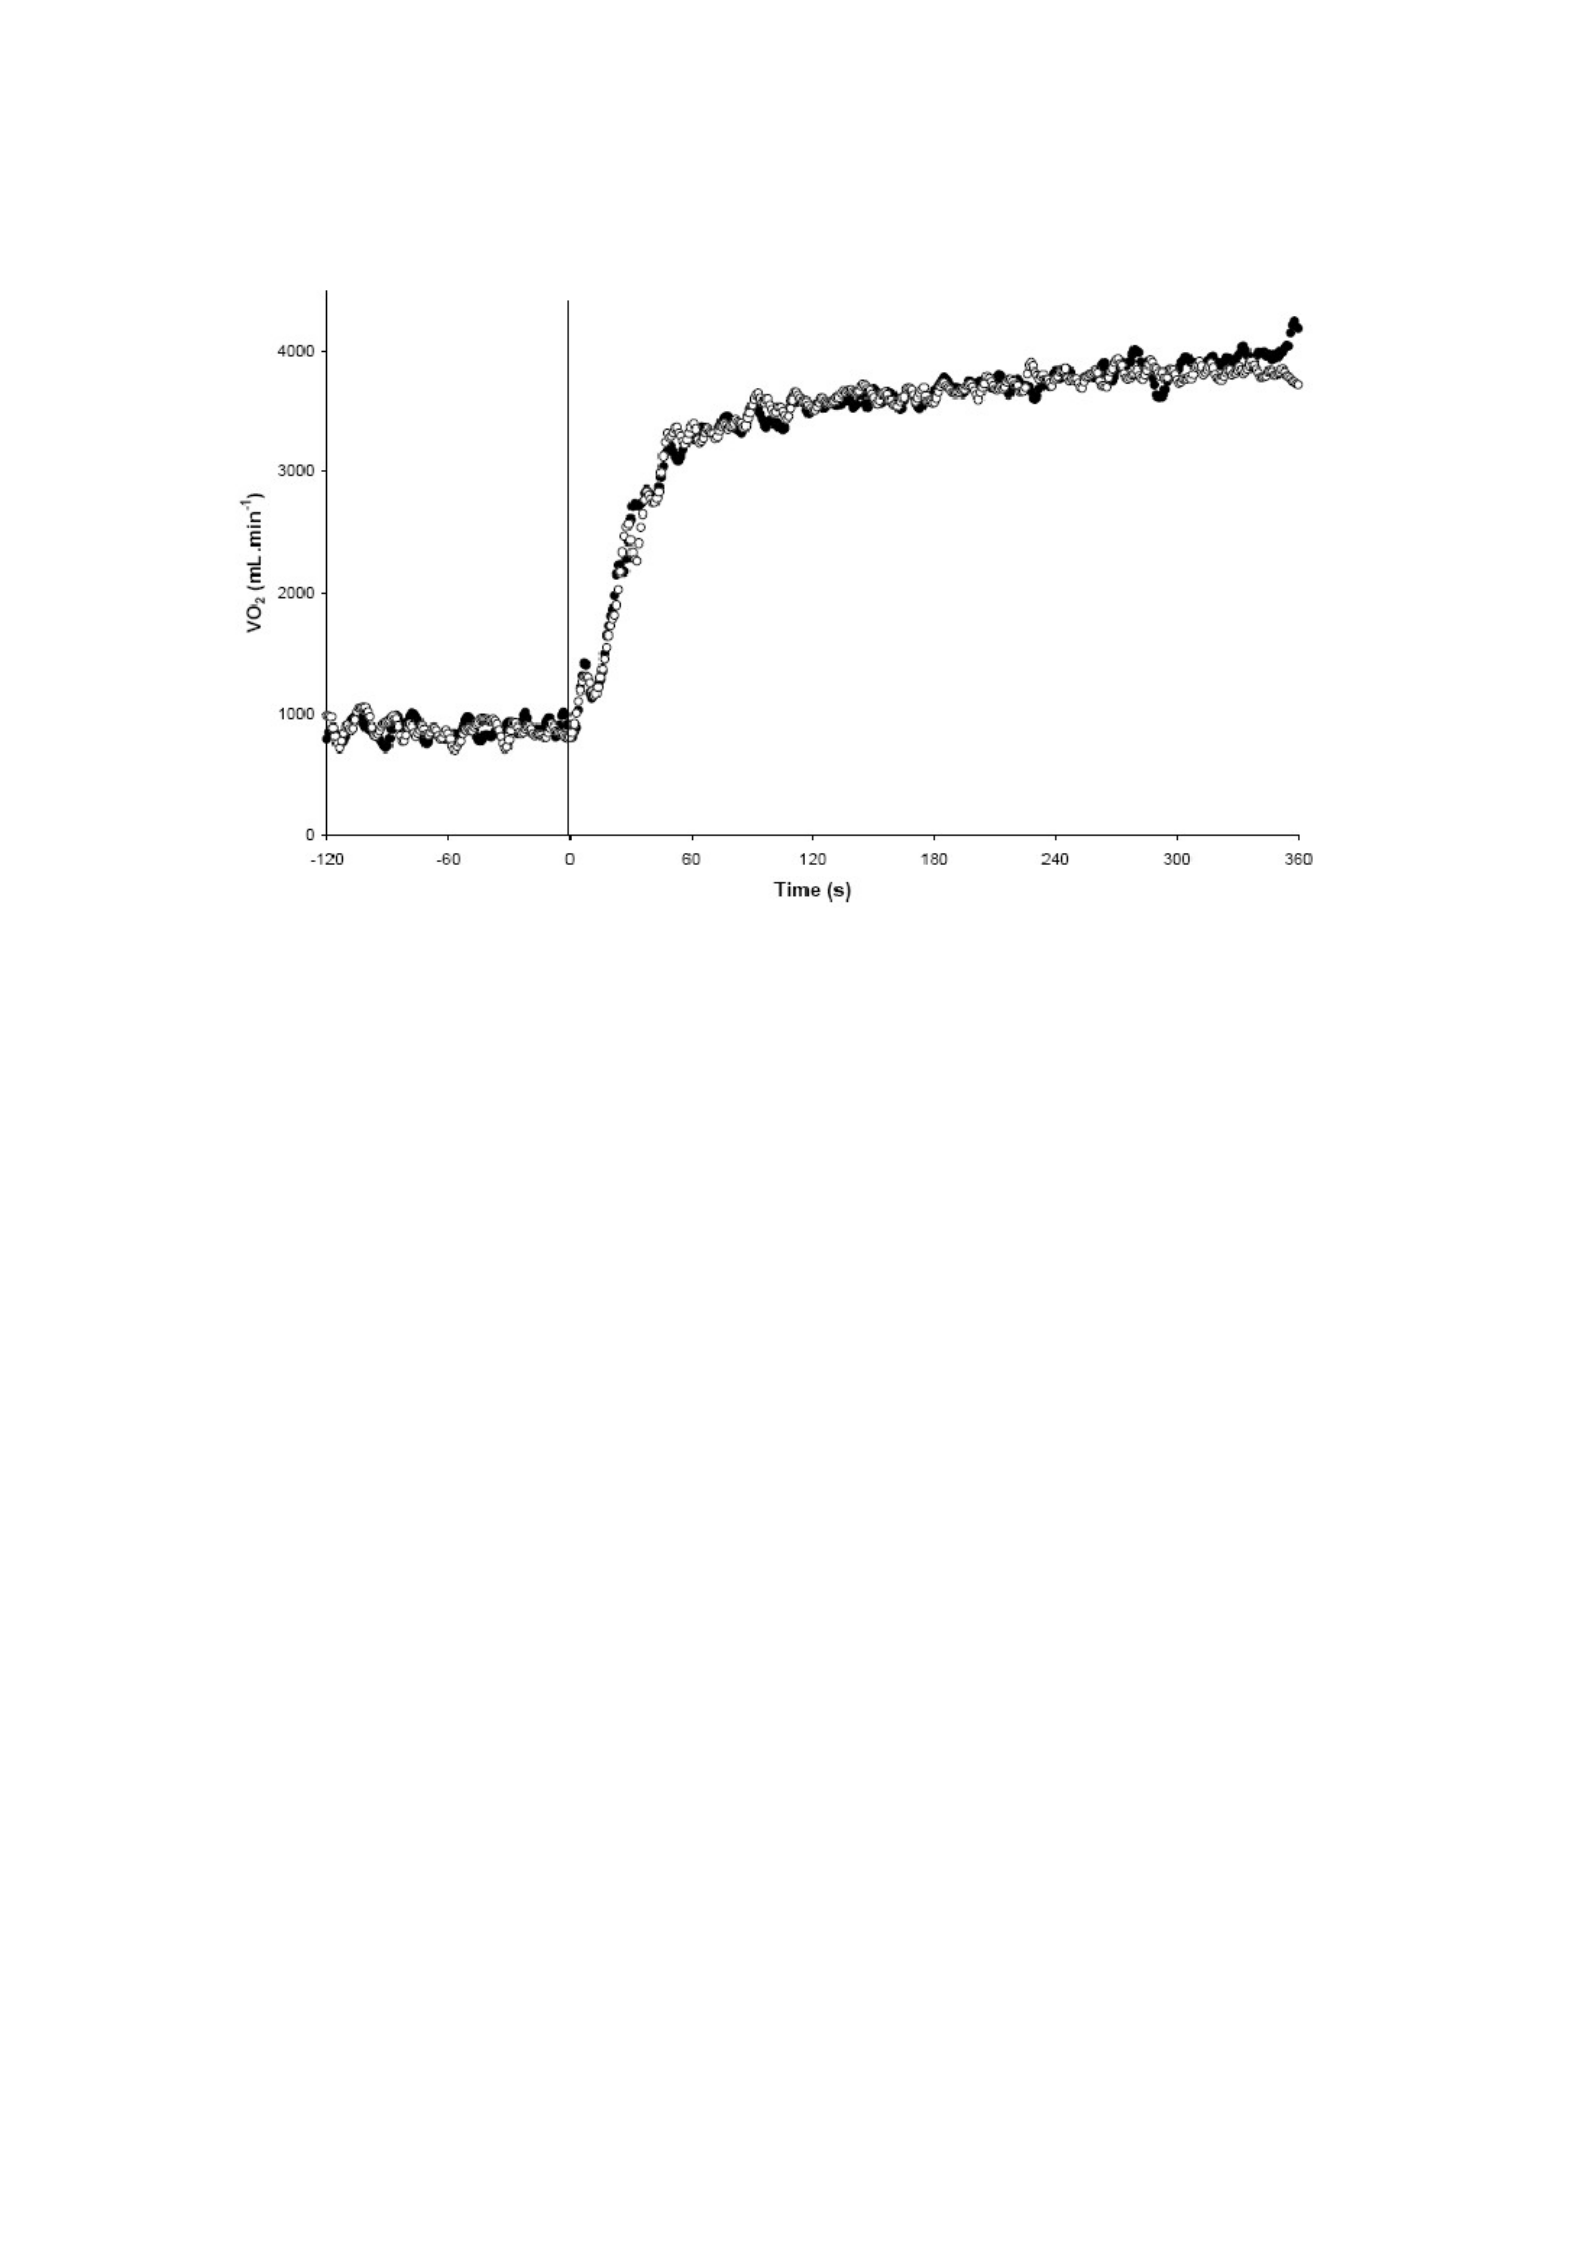
153
Figure 7.4 A representative subject’s V˙ O2 response to severe cycle exercise pre-
(●) and 48 h post- (○) eccentric exercise. The vertical line represents the transition from
‘unloaded’ to ‘loaded’ cycling.
There was a significant increase in RPE values reported during severe intensity exercise
following eccentric exercise (F (1,8) = 6.7 P < 0.05). However there were no significant
differences in the blood lactate or heart rate responses before and after eccentric exercise
(Table 7.3) (P > 0.05). In addition, there was a significant increase in the ventilatory
equivalent for O2 (/ V˙ O2 ) following eccentric exercise (pre: 29.3 (± 3.5) post: 32.6 (±
5.2))
(F (1,8) = 7.45, P< 0.05).

154
Table 7.3 Ratings of Perceived Exertion (RPE), Heart Rate (HR) and blood lactate
concentration ([La]) during severe intensity exercise pre- and 48 h post-eccentric
exercise.
baseline min
2 min
4 end
exercise
pre 48 h pre 48 h pre 48 h pre 48 h
RPE* NA NA 15 ± 1 16 ± 1 17 ± 1 18 ± 2 19 ± 1 19 ± 1
HR (b.min-1)83 ± 9 86 ± 6 159 ± 8 163 ±11 174 ±11 176 ±11 184 ± 9 181 ±11
[La] (mmol.l-1)0.9 ± 0.5 1.0 ± 0.4 3.5 ± 1.0 3.8 ± 1.0 6.9 ± 1.3 6.8 ± 1.8 8.4 ± 1.4 8.7 ± 1.8
Values are means ± SD. RPE, ratings of perceived exertion based on Borg’s 6-20 scale (Borg, 1998); HR,
heart rate; [La], blood lactate concentration; NA, not applicable.
* Significant main effect for time (P < 0.05).
There was also a significant interaction of time x test (F (9,72) = 3.15, P< 0.05) on V˙E / V˙ O2 .
Post-hoc Tukey tests indicated that
V˙
E
/ V˙ O2 was significantly greater post eccentric
exercise for the last 70% of exercise with mean values rising from 25.3 to 36.0 (pre ) and
from 26.7 to 39.9 (post) (P< 0.05).
The results of the kinetic response of [HHb] to severe intensity exercise pre- and 48 h post-
eccentric exercise are shown in Table 7.4. Most importantly, with respect to our
experimental hypothesis, both the [HHb] MRT1 and MRTt were significantly slower
following eccentric exercise (P < 0.05). There was no significant correlation between any
of the markers of muscle damage and indices of muscle oxygenation in the post damage
condition (P > 0.05). The [HHb] response of a representative subject is illustrated in Figure
7.5.
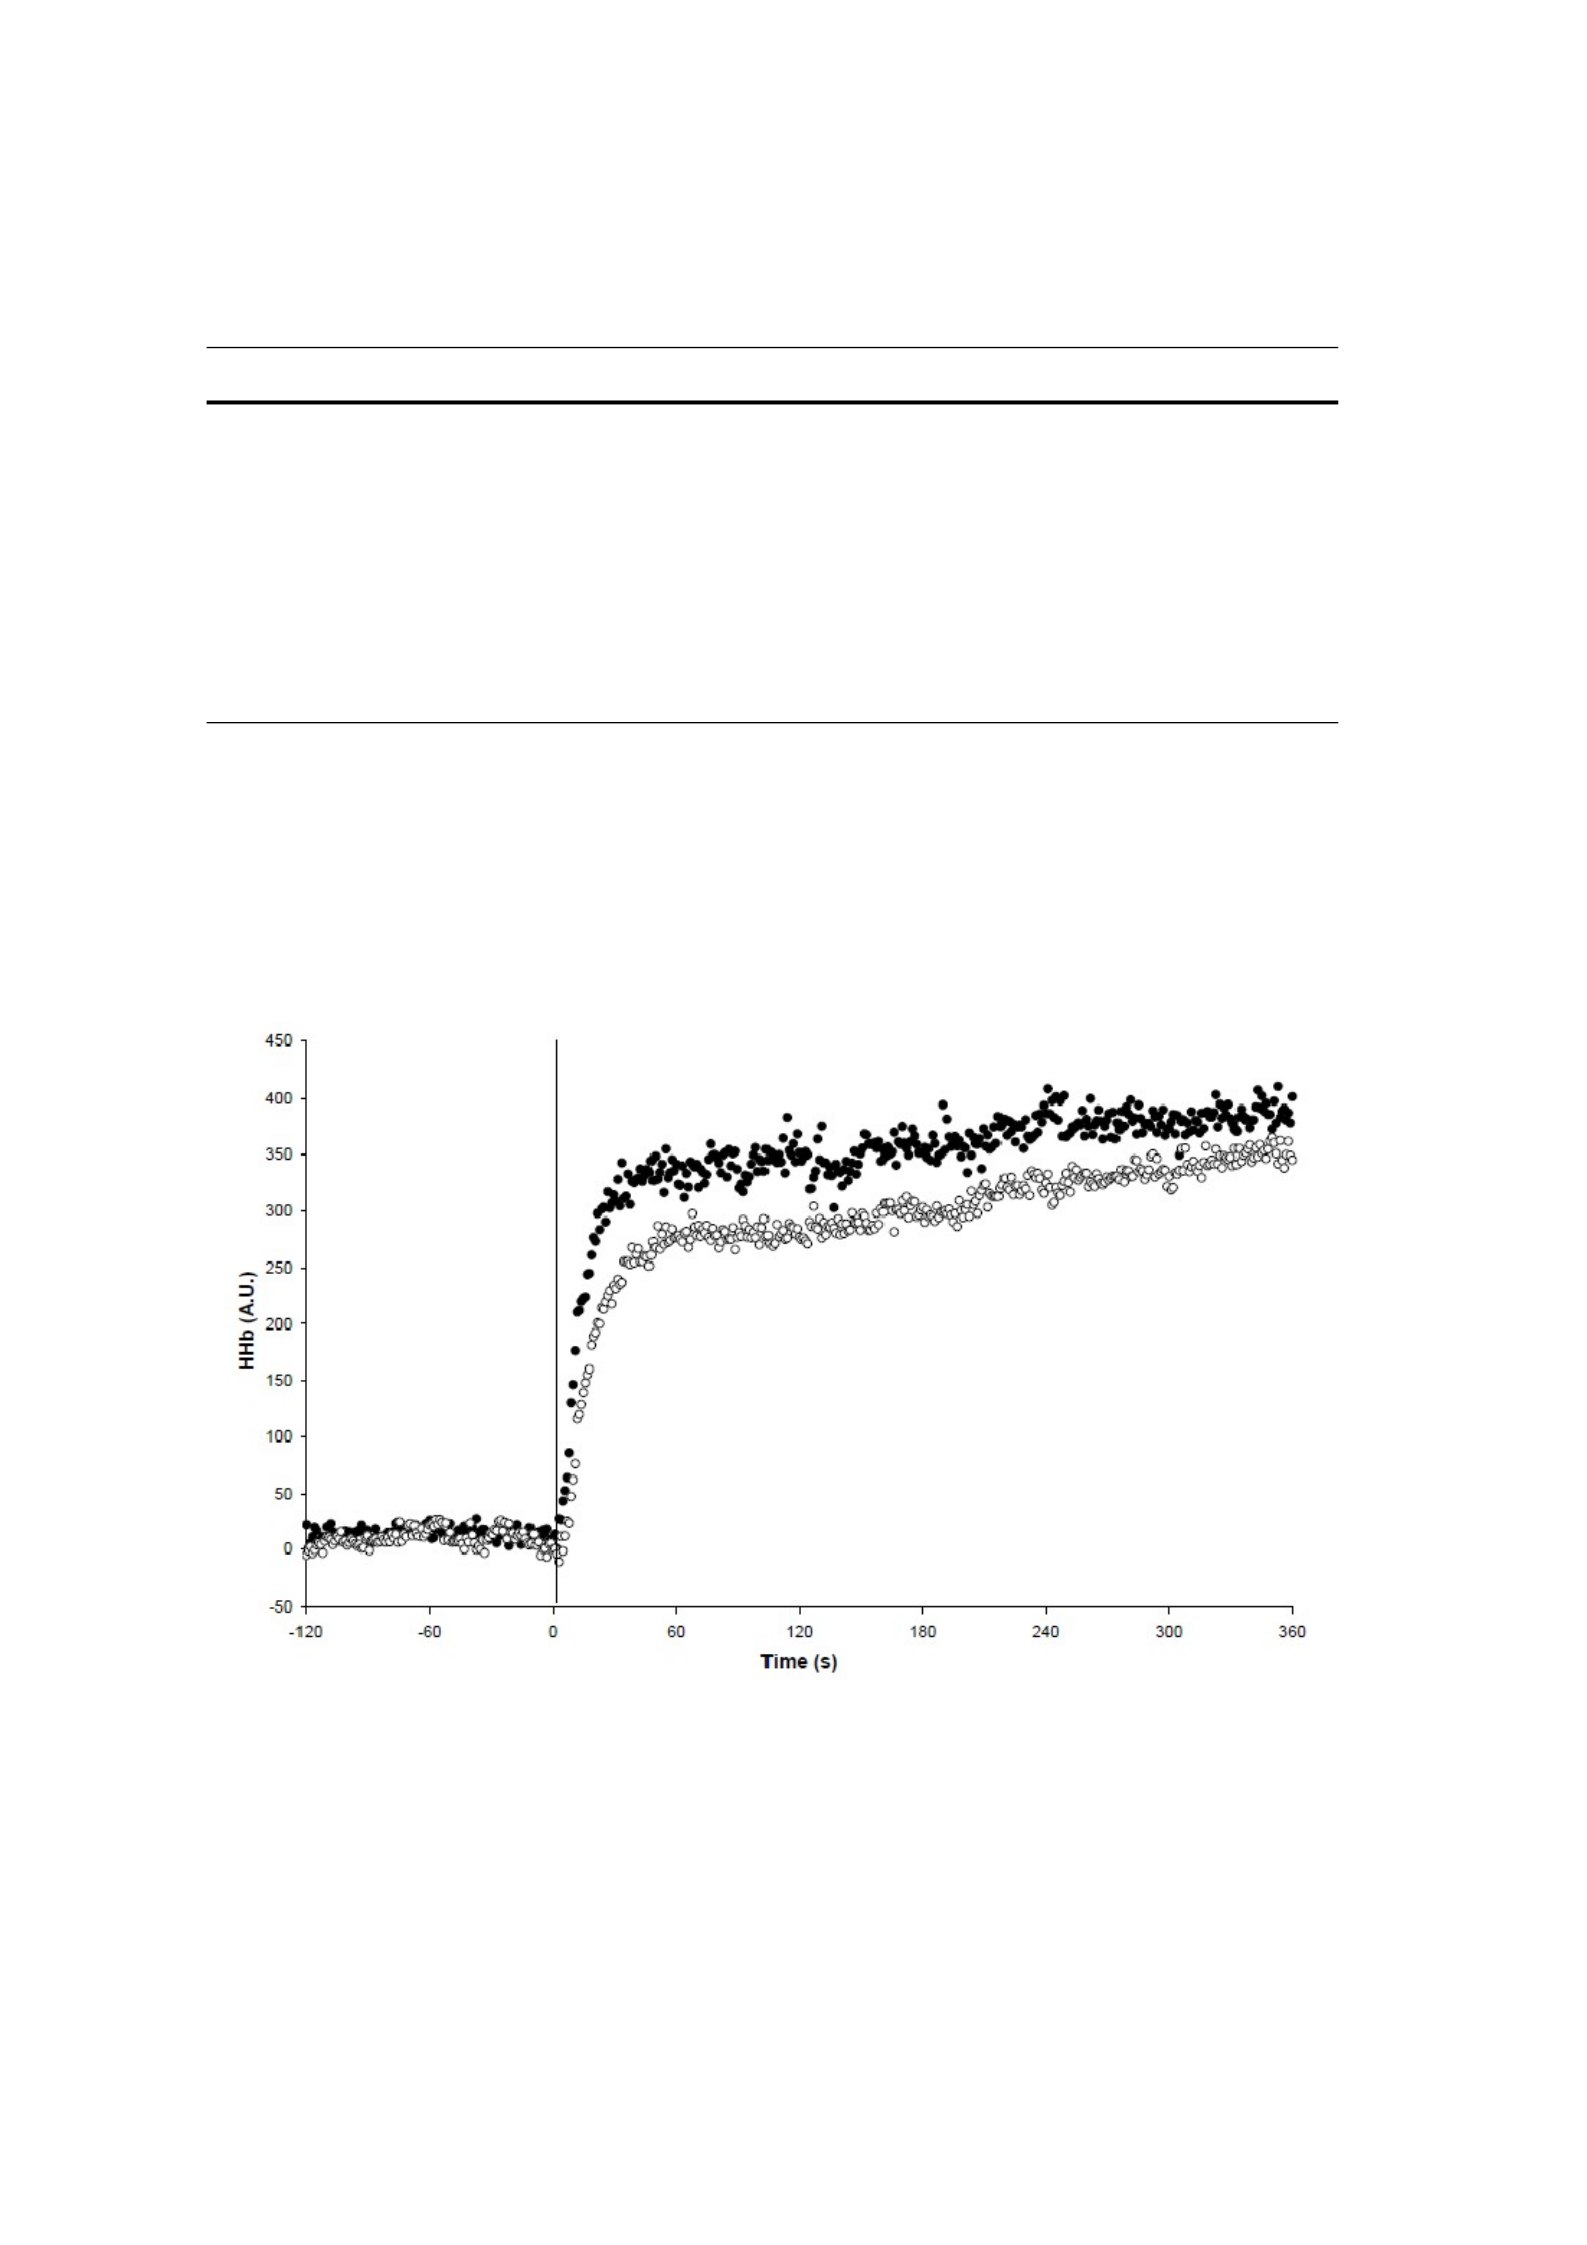
155
Table 7.4 [HHb] response to severe intensity constant-load exercise pre- and 48 h
post-eccentric exercise.
Pre 48 h
MRT1 (s) 14 ± 3 19 ± 3*
Primary Amp (%) 91 ± 8 88 ± 8
Primary Amp (A.U.) 309 ± 102 297 ± 72
MRTt (s) 16 ± 4 21 ± 4*
SC Amp (%) 9 ± 8 12 ± 8
SC Amp (A.U.) 33 ± 25 41 ± 25
Values are means ± SD. [HHb], deoxyhaemoglobin concentration; MRT1 and MRTt are the mean response
time of the primary phase (the rate of adaptation of muscle deoxygenation during the primary phase) and the
overall response (the rate of adaptation of muscle deoxygenation for the entire response), respectively.
Primary Amp is the change in [HHb] during the initial, fast increase expressed as a percentage of the overall
response (%) and as arbitrary units (A.U.). SC Amp is the change in [HHb] during the slow component (the
additional increase in [HHb] which develops slowly when exercise intensity is above the gas exchange
threshold) expressed as a percentage of the overall response (%) and as arbitrary units (A.U.)
*48 h post value significantly slower than pre value (P < 0.05).
Figure 7.5 Deoxygenated Hb ([HHb]) response to severe cycle exercise pre- (●) and 48
h post- (○) eccentric exercise in a representative subject. The vertical line represents the
transition from unloaded to loaded cycling. Note the slower overall [HHb] kinetics
following eccentric exercise (the slower rate of adaptation of muscle deoxygenation or
fractional O2 extraction, for the entire response),. AU, arbitrary units.
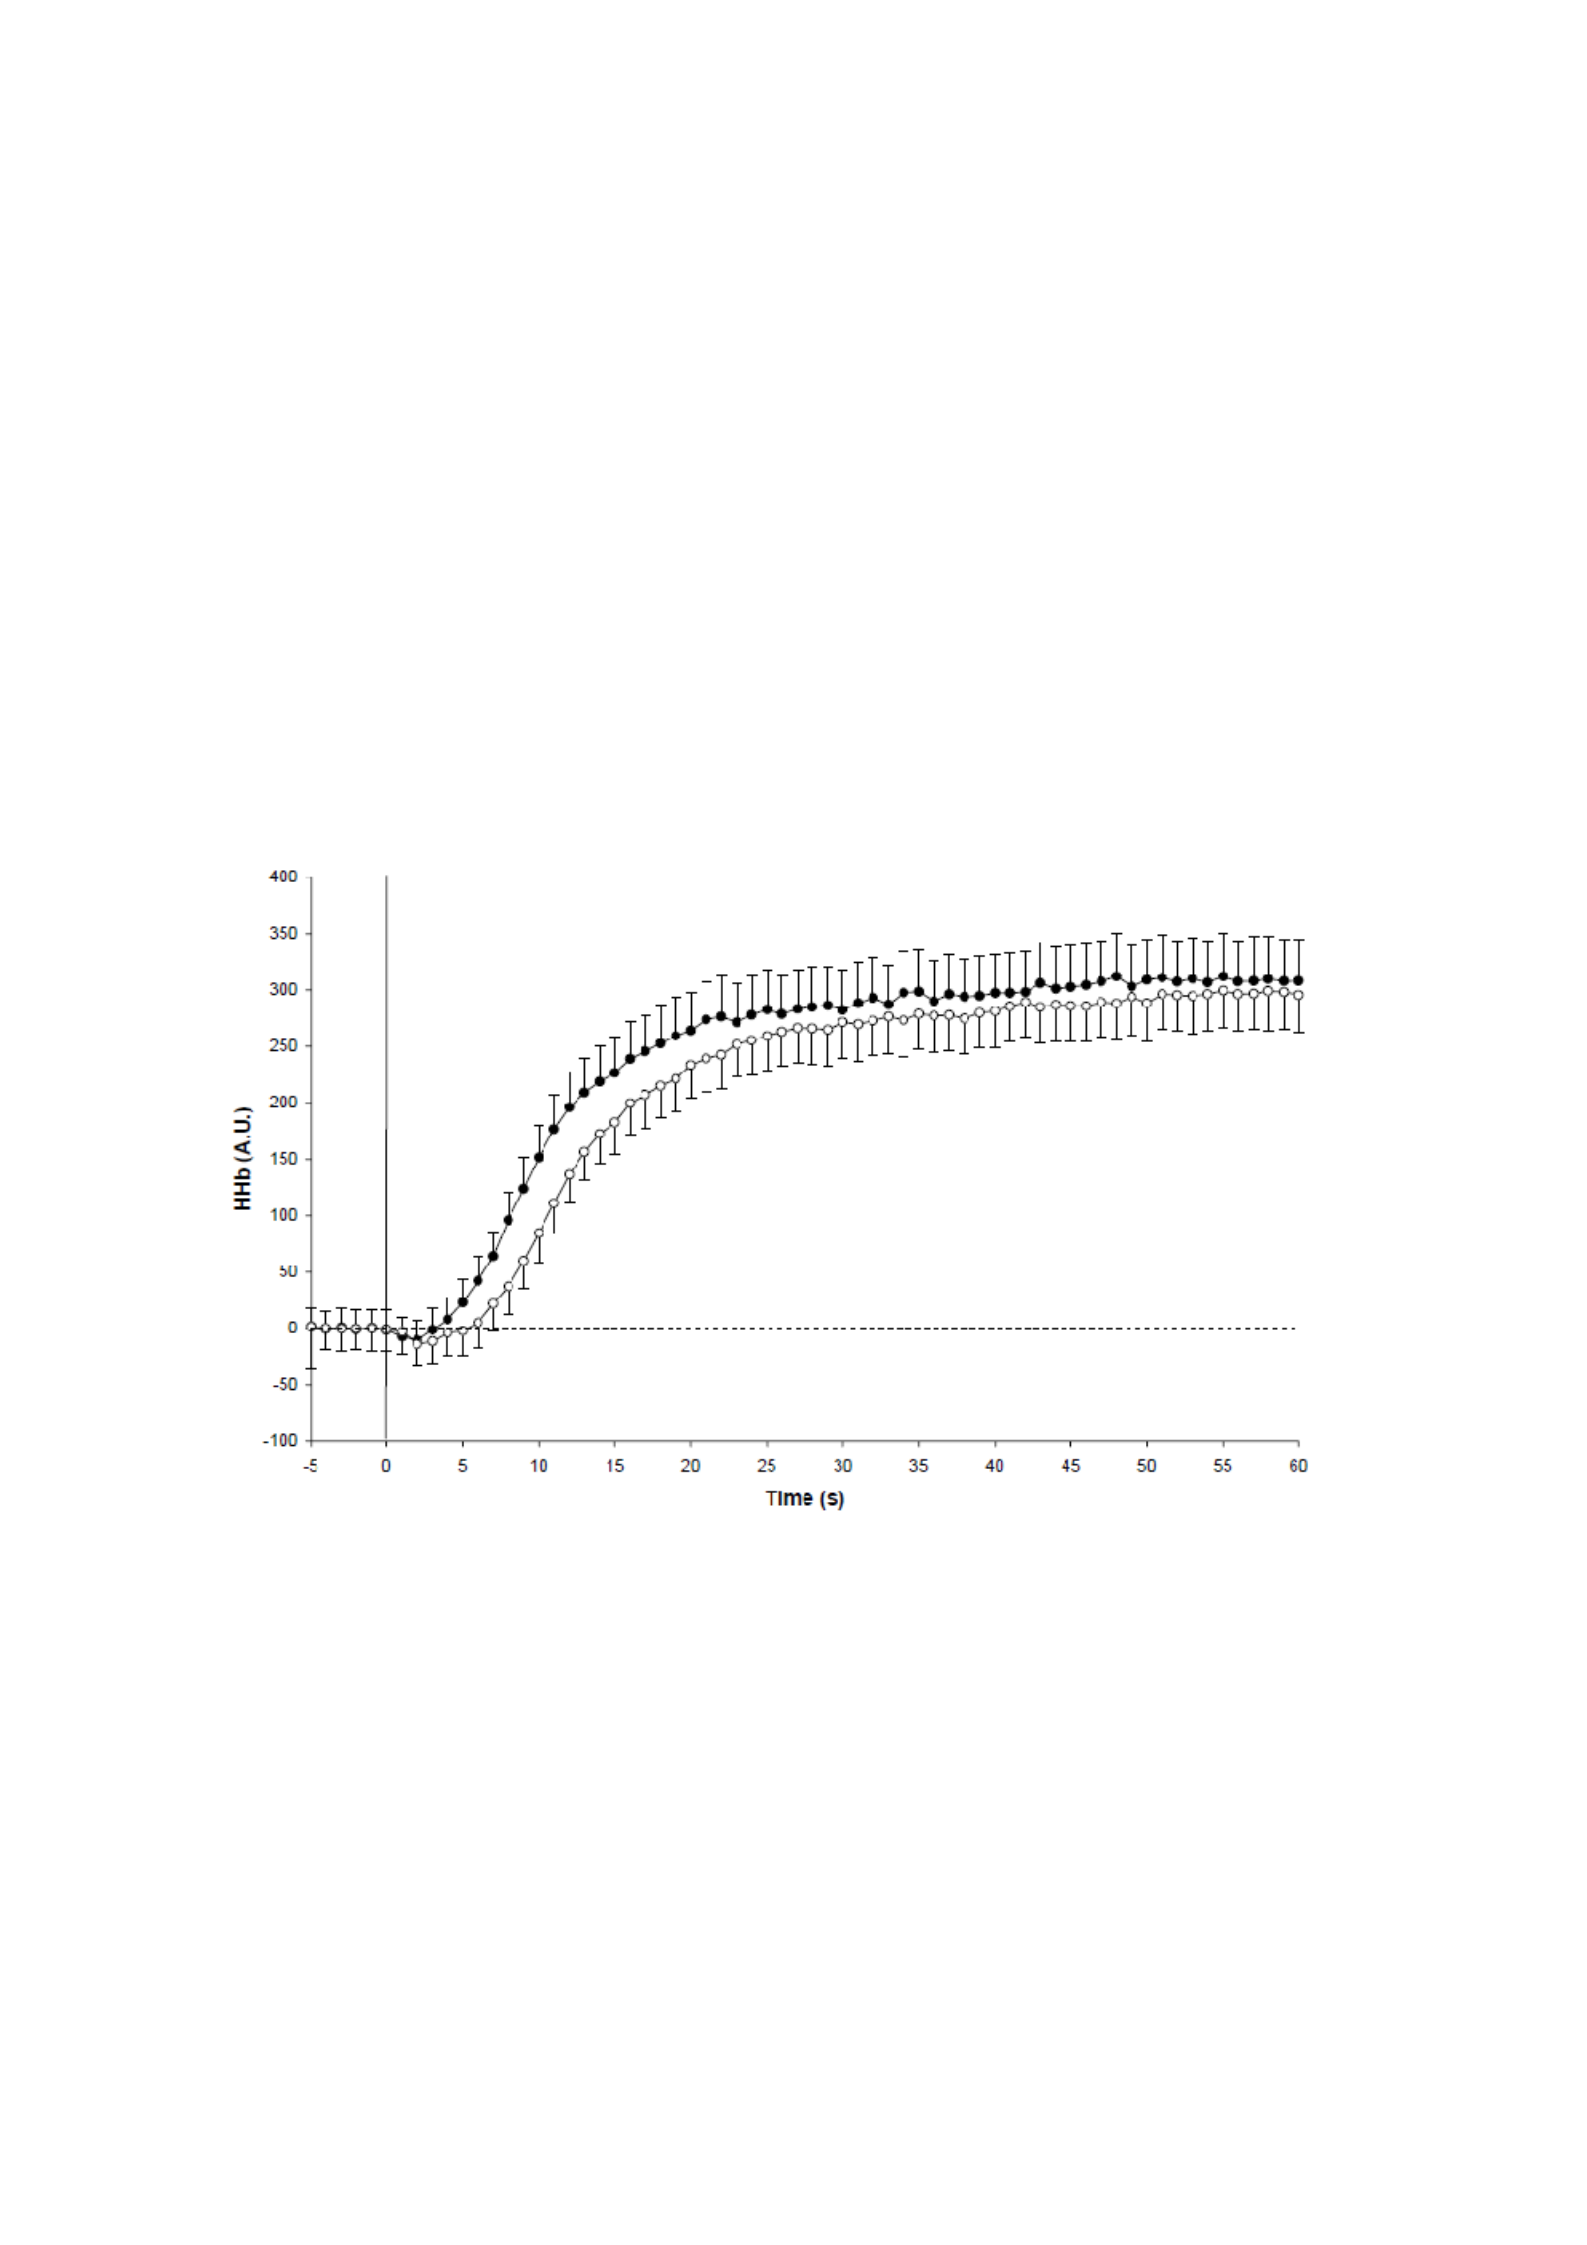
156
The altered Q˙ O2 :
V˙ O2
balance is most pronounced during the initial response following
the onset of severe intensity exercise (Figure 7.6), with the greatest mean difference
observed over the first 5-20 s (Figure 7.7). There were no significant differences in the pre-
and post-conditions between the amplitude of the response in either the primary phase or
slow component (P > 0.05). Similarly there was no difference between the total
haemoglobin responses in the two conditions (Figure 7.8).
Figure 7.6
Mean initial [HHb] response to severe cycle exercise pre- (●) and 48 h post-
(○) eccentric exercise. The vertical line represents the transition from ‘unloaded’ to
‘loaded’ cycling. The data are normalized for amplitude of the response at baseline. Values
are mean (± SE). AU, arbitrary units.
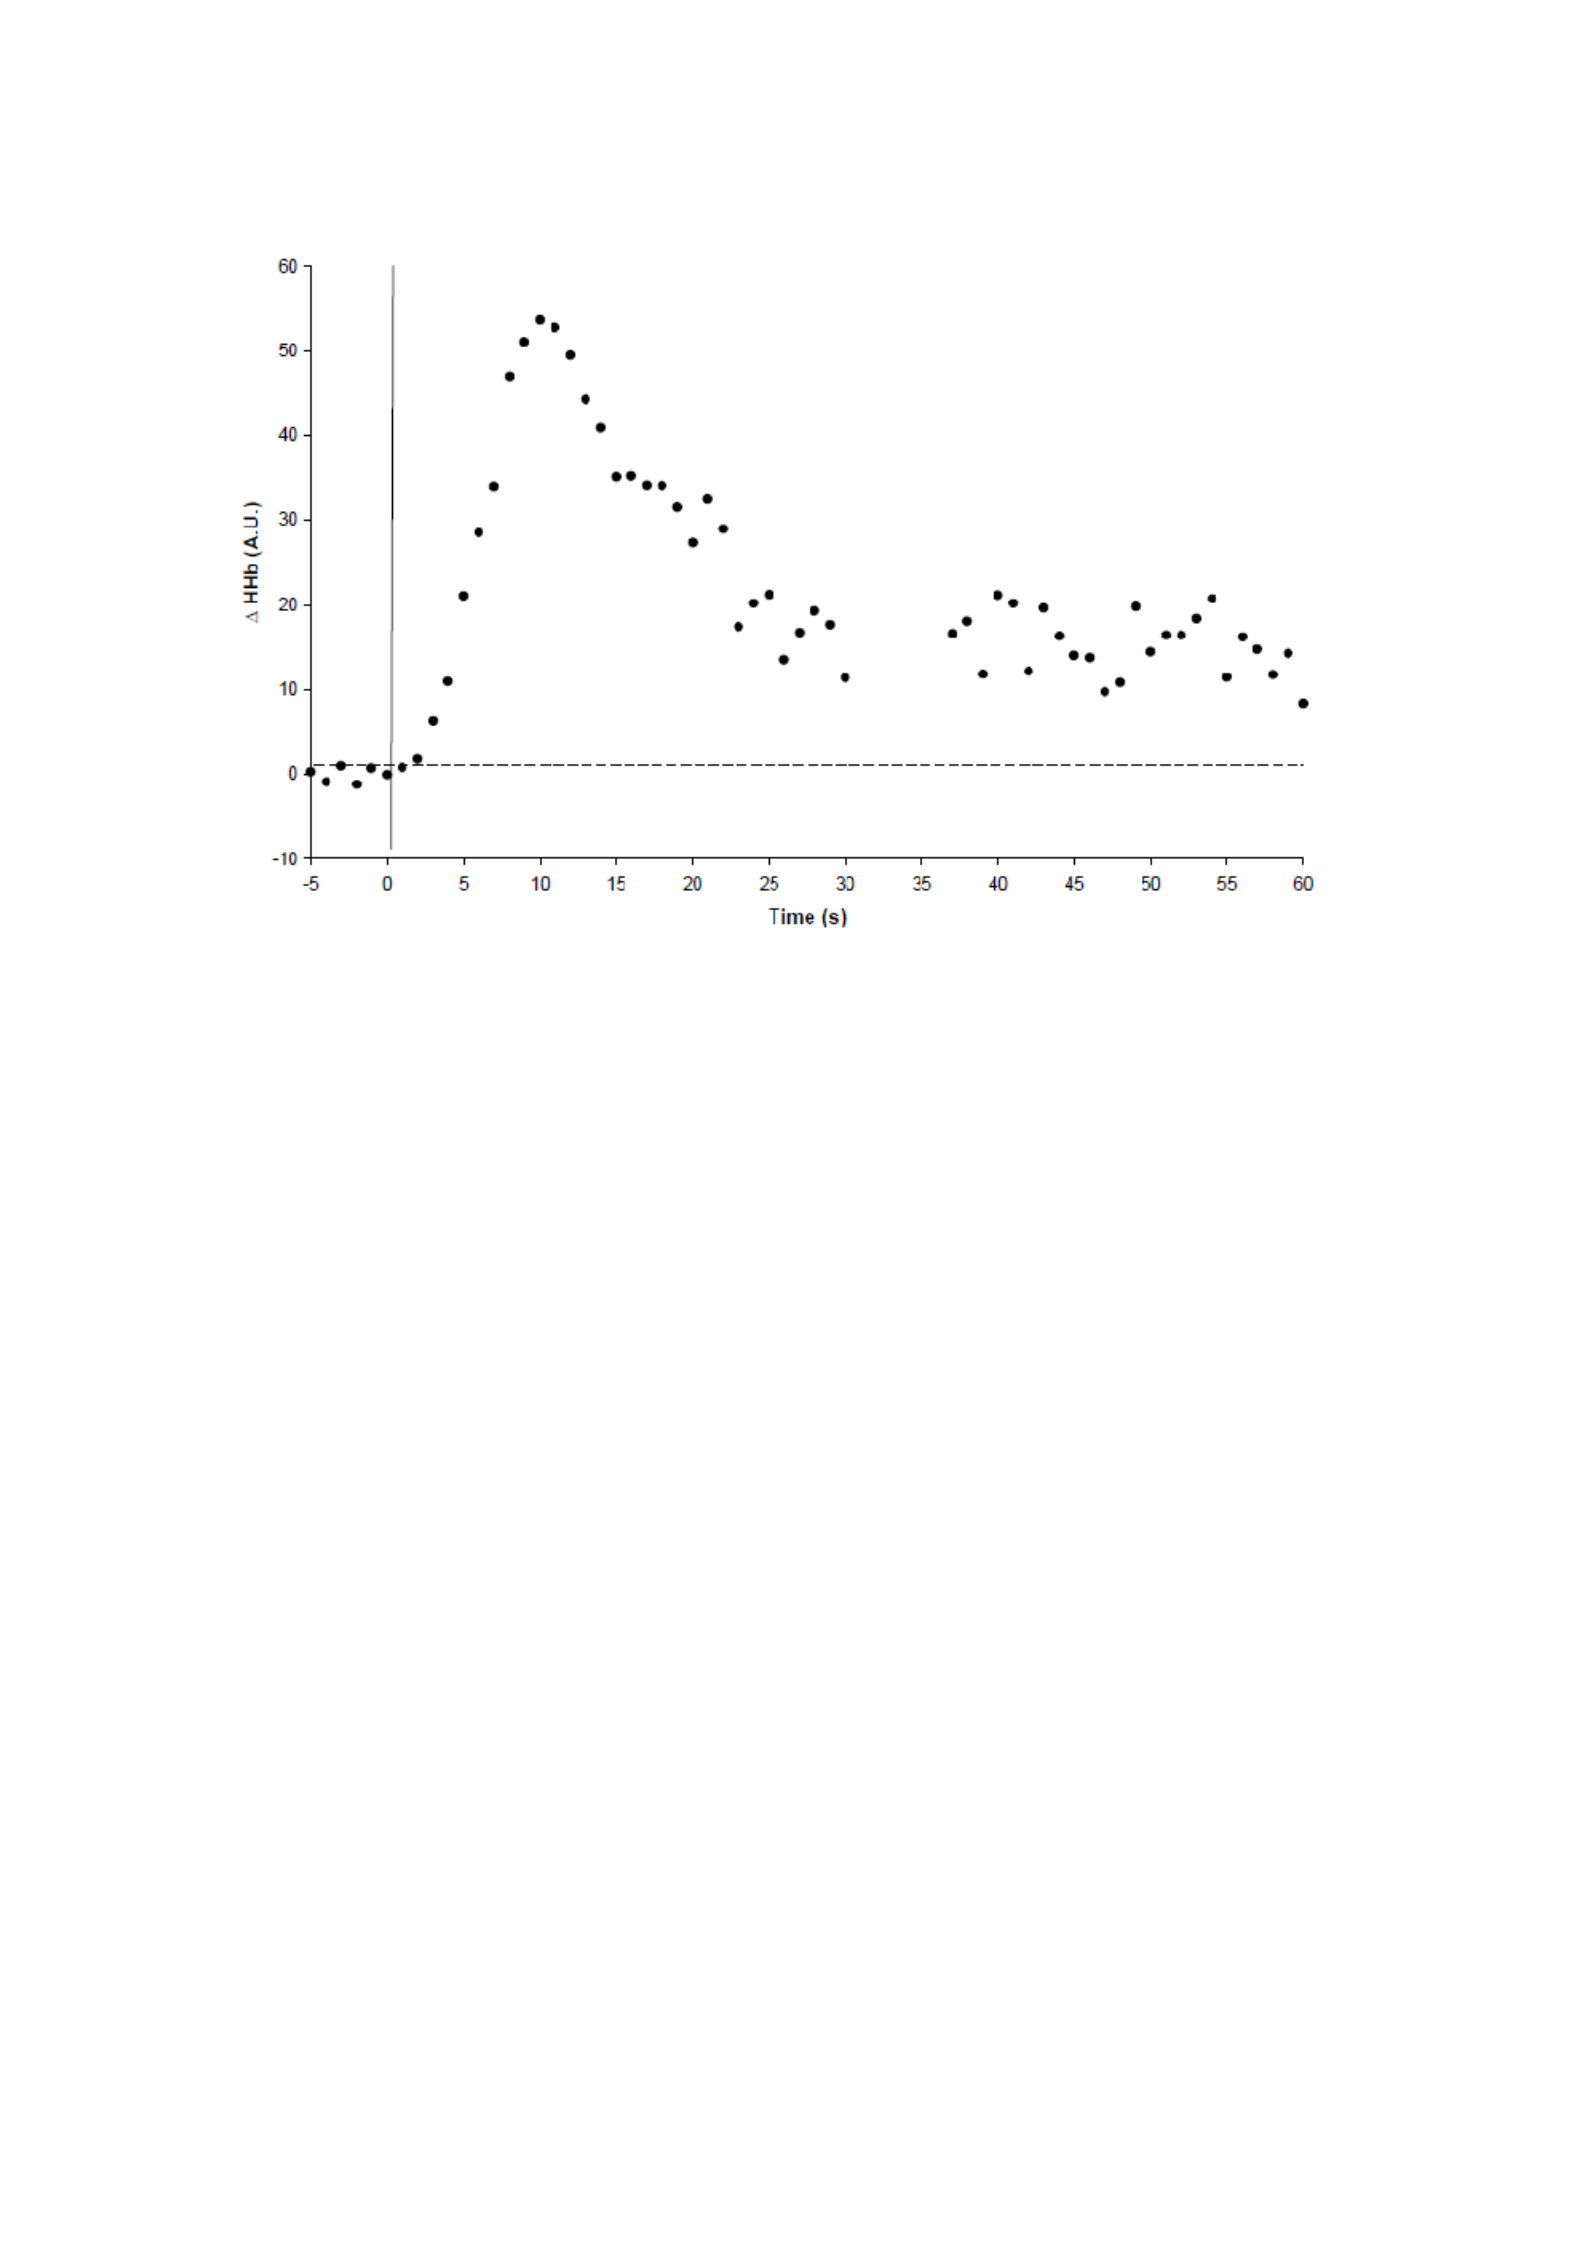
157
Figure 7.7
Mean difference in the initial [HHb] response to severe intensity exercise
pre- and 48 h post eccentric exercise (i.e. pre- minus post-eccentric exercise data). AU,
arbitrary units.
7.5 Discussion
The principal original finding of this investigation is that eccentric, muscle-damaging
exercise results in a slowing of muscle [HHb] kinetics without altering pulmonary V˙ O2
kinetics during high-intensity cycle exercise in humans. We interpret the slower [HHb]
kinetics, in the face of unchanged pulmonary V˙ O2 , to be consequent to a local elevation
of
the Q˙ O2 :
V˙ O2
ratio. The observation that the [HHb] kinetics were over 30% slower 48 h
after the performance of eccentric exercise, suggests that the matching of Q˙ O2
and
V˙ O2

158
was profoundly altered as a consequence of the intervention.
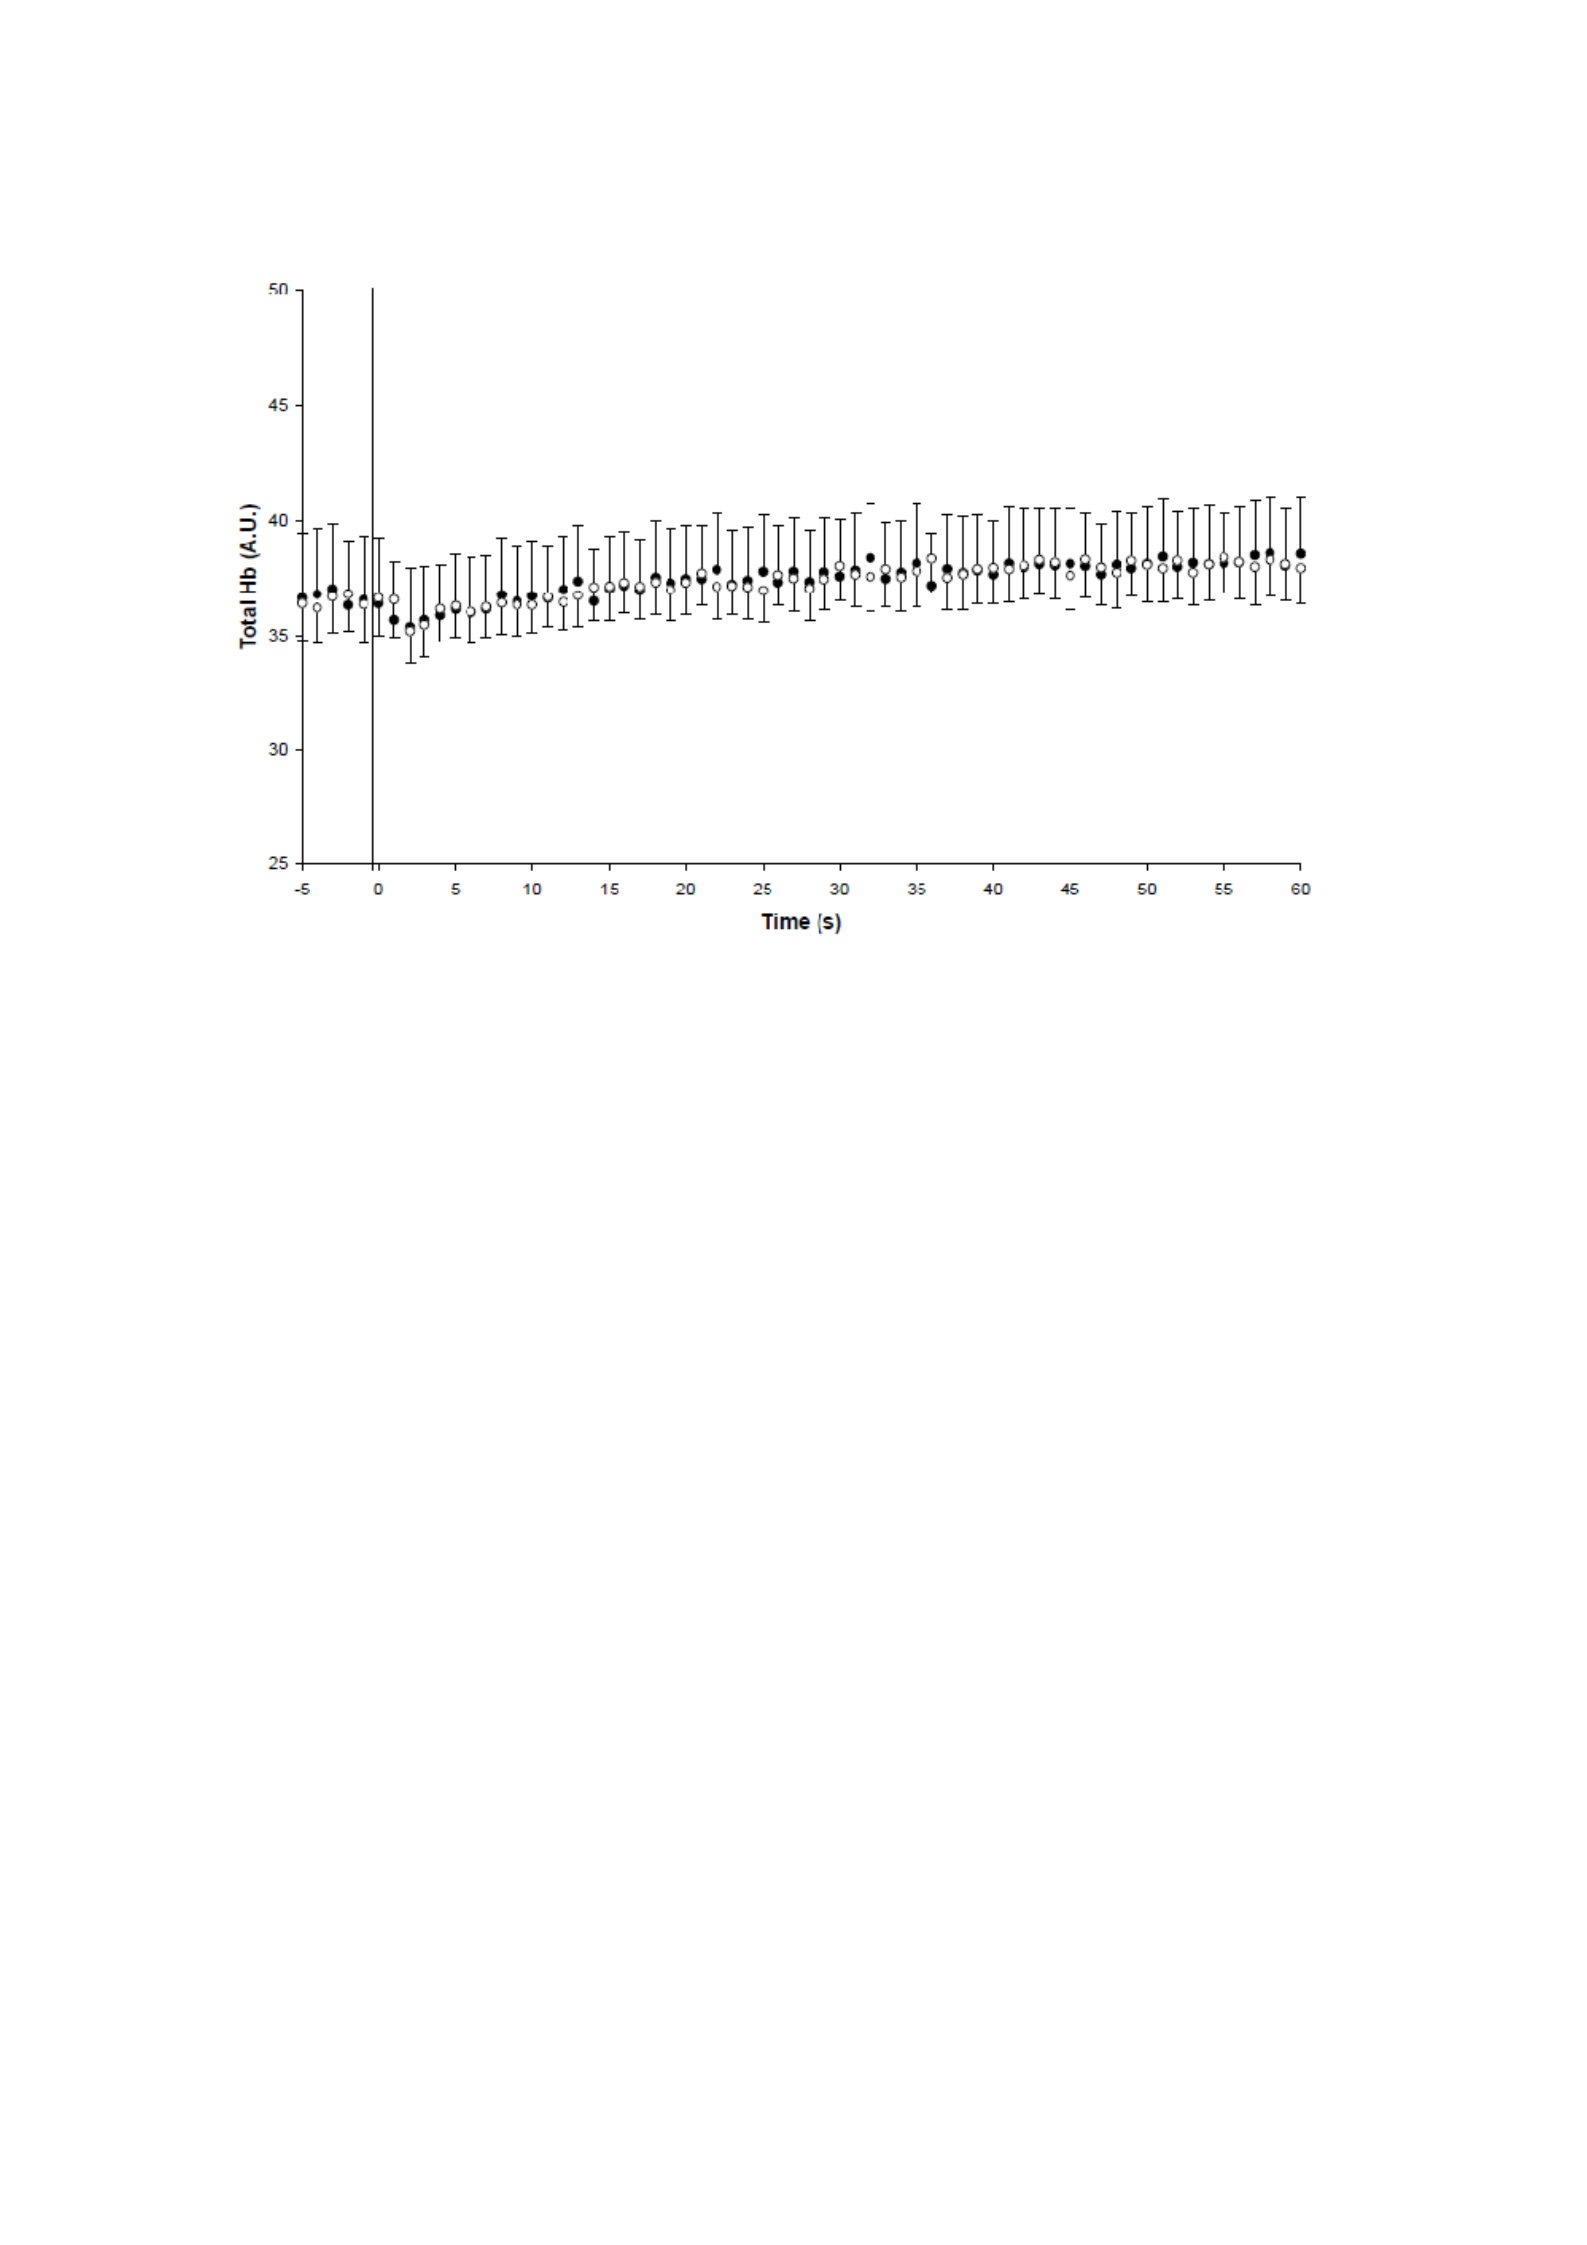
159
Figure 7.8
Total haemoglobin response to severe cycle exercise pre- (●) and 48 h post-
(○) eccentric exercise. AU, arbitrary units. Changes in total haemoglobin were not
different between conditions such that changes in [HHb] provided valid measures of muscle
deoxygenation (fractional O2 extraction). Increased blood flow, such as has been observed
by Laaksonen et al. (2006) could compensate for the decreased proportion of capillaries
supporting RBC flow such as has been observed by Kano et al. (2005) and therefore
maintain the total haemoglobin response in the area of interrogation.
The dynamic balance between O2 delivery and O2 utilisation has been keenly debated with
regard
to
possible
limitations
to
muscle V˙
O2
kinetics
(Poole
et
al.,
2008).
During
transitions to exercise intensities below GET, the compelling weight of evidence supports
the premise that metabolic inertia is the principal limitation to muscle O2 uptake (Bangsbo
et al., 2000; Grassi et al., 1998, 1996). However, for transitions to exercise intensities above
GET, the delivery of O2 may exert an additional modest constraint on muscle V˙ O2
kinetics

160
(Grassi et al., 2000, 2003; Tschakovsky & Hughson, 1999). The present data indicate that
following eccentric exercise-induced muscle damage, V˙
O2
kinetics are preserved by an

161
increase in local muscle blood flow which is presumably necessary to compensate for
microcirculatory dysfunction (Kano et al., 2005). Increased blood flow, such as has been
observed by Laaksonen et al. (2006) following eccentric exercise, could compensate for the
decreased proportion of capillaries supporting RBC flow such as has been observed by
Kano et al. (2005). In support of this thesis, we observed no change in the total
haemoglobin response, indicative of local muscle blood flow in the area of interrogation.
Thus, the changes in the [HHb] response provided valid measures of muscle deoxygenation
(fractional O2 extraction). These data therefore imply that the subjects were operating to
the right of the ‘tipping point’ (Poole et al., 2008) during the exercise bout, such that
compensatory changes in local muscle blood flow were able to prevent a measurable
slowing of V˙ O2 kinetics following muscle damage.
The squatting protocol employed herein (Byrne & Eston, 2002a, 2002b), was effective in
inducing muscle damage as indicated by the significant decreases in peak torque and
increases in plasma CK activity. Despite this, there was no significant change in phase II
V˙ O2 kinetics following eccentric exercise. These data are consistent with Schneider et al.
(2007) who reported that the V˙ O2 and HR responses to heavy-intensity cycling exercise
were unaffected by prior eccentric exercise and surmised that a moderate degree of muscle
damage did not impair O2 delivery to the active muscle or alter the
Q˙ O2 / V˙ O2 ratio.
However, indices of muscle oxygenation were not measured by these authors (60). Our
findings
contrast
with
those
of
Ahmadi
et
al.
(2008),
who
reported
faster
oxygen
desaturation (analogous to a lower Q˙ O2 / V˙ O2 ratio) during isometric contractions at 30%,
50% and 80% MVC following exhaustive downhill walking. However, differences in the

162
experimental protocol and exercise modalities employed make it very difficult to compare
the two studies. The high intramuscular pressure generated during isometric contractions is
known to impede muscle blood flow and this, or an increase in the energy demand of
contraction, might account for the faster oxygen saturation reported by Ahmadi et al.
(2008).
The experimental protocol used in the present study differs fundamentally from that
employed by Kano et al. (2005). These authors electrically induced twitch muscle
contractions (1 Hz, 3–5 V, 2-ms pulse duration) in rat spinotrapezius muscle, whereas in
our study, human subjects performed dynamic high-intensity cycle-exercise transitions.
Whilst taking these differences into consideration, it is important to note that rat
spinotrapezius muscle does provide a highly acceptable, comparative model for the analysis
of human microvascular and myocyte damage as it exhibits a fibre composition (Delp &
Duan, 1996) and oxidative capacity (Leek et al., 2001) that closely resemble that of the
human quadriceps. Thus the disruption observed in rat microvasculature subsequent to
eccentric exercise would, most likely, also be present in the damaged muscle of subjects
interrogated herein. Kano et al. (2005) reported disrupted capillary geometry and
substantial microvascular dysfunction following eccentric exercise. Specifically, an
increase in the capillary luminal area of damaged muscle was reported which resulted in a
decreased PO2mv at the onset of electrically stimulated contractions. In addition a 27–34%
increase in non-RBC-flowing capillaries was found 1–3 days after a single bout of eccentric
exercise.

163
Such structural and functional alterations to the microvasculature might act to alter the
matching of Q˙ O2 to
V˙ O2 both spatially and temporally with respect to tissue energetic
requirements.
Specifically,
the lower
[HHb]
observed
at
any
given V˙ O2 across the
transition post-eccentric exercise suggests that achievement of the requisite blood-myocyte
O2 flux might demand a higher microvascular O2 driving pressure. Blood-muscle O2 flux is
primarily determined by the number of erythrocytes lying adjacent to active myocytes at
any given time (Federspiel & Popel, 1986; Groebe & Thews, 1990). A decrease in the
proportion of capillaries supporting RBC flow would lead to a reduction in blood-muscle
O2 flux. Similarly, an increase in the diameter of free-flowing capillaries would increase the
carrier-free diffusion distance and lead to a reduction in O2 diffusing capacity.
Fick’s law of diffusion states that:
V˙O2 m = DO2 (PO2mv
–
PO2 intramyocyte)
where DO2 is the diffusing capacity for O2 and PO2mv is the microvascular O2 pressure.
Such reductions to DO2 would be expected to negatively impact V˙ O2 particularly in the
presence of concomitant alterations to PO2mv similar to those reported by Kano et al.
(2005). The O2 pressure gradient from blood to myocyte which drives O2
diffusion is
determined principally by alterations of PO2mv (Poole et al., 2006; Poole & Ferreira,
2007). Thus the accelerated fall of PO2mv observed by Kano and colleagues during the first
20–40 s of electrically stimulated muscle contractions would be expected to have a
profound influence on the muscle O2 diffusing capacity and result in a slowing of V˙ O2

164
kinetics (Behnke et al., 2004, 2007, 2006). However, the PO2mv herein (as judged by the
[HHb] response) appeared to be elevated during the dynamic rest-exercise transitions post-
eccentric exercise and the V˙ O2 kinetic response remained unchanged.
A given V˙ O2
is achieved through the interaction of O2 delivery ( Q˙ O2 ) and O2 diffusing
properties (Behnke et al., 2003). Additionally, changes in pulmonary V˙ O2 across the rest-
exercise transition are know to directly reflect leg V˙ O2 during cycling exercise (Poole et
al., 1991), and demonstrate a good approximation of the muscle V˙ O2 kinetics (Grassi et al.,
1996). Therefore, the elevated
Q˙ O2 : V˙ O2 ratio evidenced by the slower [HHb] kinetic
response (i.e. lower [HHb] at a given V˙ O2 across the exercise transition) must, in this
instance, be due to compensatory changes to O2 delivery (see Appendix J). Pertinent to this
issue, increased blood flow (and therefore increased O2 delivery) has been observed by
Laaksonen et al. (2006) who found that blood flow to the exercising Quadriceps femoris
was elevated by 25% after a prior bout of exhaustive eccentric exercise. Importantly, they
also reported that
V˙ O2 remained unchanged and suggested that the altered
Q˙ O2 : V˙ O2
balance observed may have been due to impaired oxygen extraction. Thus, following
eccentric muscle-damaging exercise, adaptive, compensatory mechanisms may act to
elevate PO2mv across the rest-exercise transition, preserving blood-myocyte O2 flux as
indicated by the unchanged phase II V˙ O2 kinetics.
The higher ratings of perceived exertion reported for a given exercise intensity (70 %∆)
following eccentric exercise may be due, in part, to the enhanced ventilatory response

165
which accompanies the increased muscle soreness. It has been proposed that an altered

166
sense of effort may be part of a central protective mechanism whereby neural inhibition
serves to reduce force generation in order to prevent further injury (Kyrolainen et al., 2000;
Michaut et al., 2002; Proske et al., 2004). Additionally, Hotta et al. (2006) suggested that
changes in neural factors contribute not only to alterations in force generation but also to an
enhanced ventilatory response. Group III and IV afferent fibres located in and around the
blood vessels of exercising muscle are involved in modulating the ventilatory response.
Distension of these blood vessels provokes a discharge from the afferent fibres that leads to
an increase in ventilation (Haouzi et al., 2004, 1999). Thus, neural monitoring of peripheral
vascular events might account, in part, for the enhanced / V˙ O2 observed in this study if
there were alterations to the microvasculature as a result of eccentric exercise. Pertinent to
this issue, in studies employing male Wistar rats, Kano et al. (2004) have reported changes
in the capillary lumen shape (luminal ellipticity) that increase the luminal cross-sectional
area by up to 62% following eccentric exercise. Similar increases in the cross-sectional area
of the microvessels in the muscles recruited in the present investigation might serve to
augment the ventilatory response via neural modulation.
It has been proposed that, following eccentric exercise, alterations to motor unit recruitment
patterns arise in order to meet the energetic demands of a given work rate (Clarkson, 1992).
Reports of elevated blood lactate concentration following eccentric exercise have been
attributed to the additional recruitment of type II fibres and a concomitant rise in the rate of
glygogenolysis (Chen et al., 2007b; Gleeson et al., 1998). However, Chen (2003) reported
that neural adaptation to motor unit activation patterns occurred after a single bout of
eccentric exercise, such that additional type I motor units were recruited. Additional fibre
recruitment has been implicated in the development of the V˙ O2 slow component in high-

167
intensity exercise (Krustrup et al., 2004). Specifically, it has been proposed that the
development of a
V˙ O2 slow component may be related, in part, to the recruitment of
additional type II fibres (Barstow et al., 1996; Pringle et al., 2003; Whipp, 1994). The
reduction in the amplitude of the V˙ O2 slow component observed herein may therefore be
indicative of an altered motor unit recruitment pattern consequent to muscle damage
(Pringle et al., 2003). However, the unchanged primary V˙ O2 response and the unchanged
blood lactate concentration observed are arguably not in keeping with this suggestion.
Additionally, full expression of the slow component may have been impeded as a result of
muscular fatigue and a reduction in maximal work capacity brought about by the effects of
eccentric exercise. Such impediments to performance have previously been reported to
result in a shorter time to exhaustion in mice (Carmichael et al., 2005, 2006) and a reduced
time trial running distance in human subjects (Marcora & Bosio, 2007). Accordingly, the
reduction in the V˙ O2 slow component observed post-eccentric exercise may be attributed
to a shorter time to exhaustion and a tendency for a lower V˙ O2 peak to be achieved in this
condition.
Experimental considerations
As mentioned earlier, our findings contrast with those of Kano et al. (2005) due to
fundamental differences in the muscle activation processes employed rather than species
variation. We studied dynamic exercise transitions to severe intensity (70 %∆) cycle
exercise, whereas Kano and colleagues utilised a set rate of electrical stimulation (1 Hz, 3–
5 V, 2-ms pulse duration) to induce muscle contractions. Electrical stimulation induces
recruitment of all fibres, whilst voluntary exercise recruits specific fibres and fibre types

168
dependant on exercise intensity and duration (Kindig et al., 2002). Thus, the muscle
activation and attendant fibre recruitment patterns studied herein present a more
ecologically valid model for investigation. As such, this study may provide a more realistic
insight into the effects of eccentric muscle-damaging exercise on functional human
performance.
NIRS is an established technique for the measurement of muscle oxygenation (e.g. Ferrari
et al., 2004; Jones et al., 2006). However, the reliability and reproducibility of the NIRS-
derived [HHb] signal is dependant on the precise placement of the optodes. In the present
study, optode location was marked on each individual subject during the first visit to the
laboratory and placement was carefully reproduced on subsequent visits. Koga et al. (2007)
have revealed the presence of significant heterogeneity with respect to the dynamics of
muscle oxygenation within the quadriceps muscles of healthy subjects following the onset
of exercise. These findings are not surprising given that muscle blood flow, motor unit
distribution and recruitment and consequently vascular responses are known to be
heterogeneous within and across muscles. However, it is important to recognise that the
NIRS data reported herein is representative of changes within the superficial muscle area
under interrogation only and as such may not be representative of the entire muscle mass
affected by eccentric exercise.

169
7.6 Conclusion
In conclusion, the present investigation suggests that eccentric, muscle-damaging exercise
alters the matching of Q˙ O2 and V˙ O2 during severe intensity exercise. Specifically, across
the rapid metabolic transition following the onset of exercise, for a given V˙ O2 , the [HHb]
signal is reduced. We propose that structural and possibly functional alterations to the
microvasculature act to increase the Q˙ O2 : V˙ O2 ratio both spatially and temporally with
respect
to
tissue
energetic
requirements.
Accordingly,
following
eccentric
muscle-
damaging exercise, compensatory mechanisms act to elevate the microvascular driving
pressure for blood-myocyte O2 flux, enabling a preservation of the kinetics of V˙ O2 across
the rest-to-exercise transition.

170
CHAPTER 8
CONCLUSIONS

171
8.1 Main Findings
8.1.1 The ventilatory response to dynamic exercise with EIMD
Previous investigations have reported that the ventilatory response to running exercise is
unchanged following EIMD (Paschalis et al., 2005; Scott et al., 2003; Marcora and Bosio,
2007). Other investigations that reported an increased ventilatory response and an elevated
blood [La] response during running attributed the changes to altered lower limb kinematics
(Braun & Dutto, 2003; Chen et al., 2007b, 2008). During cycle exercise, where the
potentially confounding influence of altered kinematics is avoided, increases in both
ventilation and blood [La] have been reported (Gleeson et al., 1995; Schneider et al., 2007).
Prior to the studies which comprise this thesis being undertaken, Schneider et al. (2007),
using an exercise intensity of 40%∆, provided the only example of an investigation using a
specific exercise domain to study the influence of EIMD on physiological responses to
dynamic exercise.
The findings of studies 1 (Chapter 4) and 4 (Chapter 7) demonstrated that the ventilatory
response to cycle exercise was elevated 48 h after eccentric exercise (100 squats with a load
corresponding to 70% of body mass). Importantly, ventilation was increased not only
during severe intensity (70% ∆) cycle exercise but also during moderate intensity (80%
GET) cycle exercise without any significant change in the blood [La] response. Previously,
it had been assumed that an increase in [La] contributed to an augmented ventilatory
response. However, our findings, in particular the observation that the ventilatory response
following EIMD is higher during exercise below GET, suggest that the altered exercise
response may not be due to changes in metabolic factors. Rather, we propose that neural
monitoring of peripheral vascular and local muscular events may, in part, account for the

172
augmented ventilatory response observed. The mechanisms involved in ventilatory control
during exercise are complex and involve a combination of central command and afferent
feedback. However, the structural and functional changes that characterise EIMD are
understood to augment discharge from group III and IV afferents. These changes rather
than elevated blood [La] which is not an obligatory consequence of EIMD, most probably
contribute to the greater ventilatory response to dynamic cycle exercise evoked by EIMD.
8.1.2 The Gas Exchange Threshold (GET) and EIMD
During dynamic incremental exercise protocols, identification of the GET provides the
basis for the non-invasive estimation of the lactate threshold (Tlac) (Beaver et al., 1986;
Caiozzo et al., 1982; Wasserman et al. 1973, 1990). However, the ventilatory and lactate
responses to incremental exercise may be dissociated by various experimental and clinical
conditions (e.g. Poole & Gaesser, 1985; Hughes et al., 1982; Hagberg et al., 1982). It was
our contention that EIMD was likely to exacerbate the ventilatory response to
incremental/ramp exercise and, in so doing, potentially dissociate the ventilatory, gas
exchange and lactate responses.
The findings of study 2 (Chapter 5) demonstrated that 48 h after eccentric exercise GET
occurred at a lower work rate (pre, 136 ± 27 W; post, 105 ± 19 W, P< 0.05) and V˙ O2 (pre,
1.58 + 0.26; post, 1.41 + 0.14 l.min-1, P< 0.05). However, the lactate threshold occurred at
a similar work rate (pre, 161 ± 19 W; post, 158 ± 22 W, P> 0.05) and V˙ O2 (pre, 1.90 ±
0.20 l.min-1; post, 1.88 ± 0.15 l.min-1, P > 0.05) after eccentric exercise. These findings
demonstrated that EIMD dissociates the ventilatory response to incremental exercise from
the blood [La] response. Thus, these findings provide further evidence to support the thesis

173
that ventilation may be controlled by additional or altered neurogenic stimuli following
eccentric exercise.
8.1.3 The perception of exertion during dynamic exercise with EIMD
Irrespective of the mode of damage, the exercise intensity, or exercise protocol employed,
eccentric, muscle-damaging exercise is known to evoke an increased sense of effort
(Gleeson et al., 1995; Scott et al., 2003; Marcora & Bosio, 2006; Twist & Eston, 2009).
The cues which inform the perceptual response to exercise may arise from central or
peripheral sensations, with the influence of central (cardiorespiratory) cues of lesser
importance than that of local (muscle) sensations, particularly at lower exercise intensities
(Mihevic, 1981; Hampson et al., 2001). As such, the perception of exertion reported during
exercise with EIMD may be differentially influenced by central and peripheral cues
dependent on the exercise intensity.
During ramp/incremental cycle exercise in study 3 (Chapter 5) participants reported a
higher perception of exertion at 48 h, with an increase in reported RPE of 7% observed at
the V˙
O2
value of the pre-eccentric exercise GET. In studies 1 and 4 (Chapters 4 and 7)
participants reported higher ratings of perceived exertion (RPE) during constant-load,
severe intensity (70%∆) cycle exercise 48 h after eccentric exercise, although RPE
appeared to be unchanged during moderate (80% GET) exercise. It was of interest that the
increased muscle pain and the elevated ventilatory response experienced by participants at
48 h did not significantly influence the perception of exertion during moderate intensity
exercise. However, during severe intensity exercise, where the central, ventilatory cues may
have played a more influential role in informing the perception of exertion, RPE was

174
significantly higher. In study 1 (Chapter 4) minute-by-minute differences in RPE values
reported during severe exercise to volitional exhaustion before and 48 h after eccentric
exercise were eliminated when expressed as a percentage of total exercise duration. This
observation provided further evidence to support the proposition that there is a scalar-linear
relationship between the rating of perceived exertion and exercise duration. Furthermore,
differences in ventilation were also eliminated when expressed as a proportion of time to
exhaustion. These findings suggest that there is a strong link between the ventilatory and
perceived exertion responses to cycling following eccentric exercise.
8.1.4 Time to exhaustion
The perception of exertion may be considered fundamental to the individual exercise
response when a participant is required to exercise to ‘volitional exhaustion’. Observations
of elevated RPE have previously been associated with reduced time-trial performance in
running and cycling following EIMD (Marcora & Bosio, 2007; Twist & Eston, 2009).
During incremental cycle exercise in study 2 (Chapter 5) and incremental knee extensor
exercise in study 3 (Chapter 6) the observed decrease in time to volitional exhaustion and
the associated reduction in peak work rate values were consistent with observations of
impaired time trial performance brought about by the effects of eccentric exercise.
Similarly, in studies 1 and 4 (Chapters 4 and 7) time to exhaustion was reduced following
eccentric exercise, during constant load cycling at an intensity of 70%Δ. The precise nature
of the accelerated fatigue development experienced with EIMD is poorly understood. Both
central and peripheral fatigue factors have been implicated in the decreased endurance
capacity observed following EIMD.

175
8.1.5 The metabolic response to dynamic exercise with EIMD
Central fatigue factors such as the enhanced production of inflammatory cytokines within
regions of the brain responsible for movement, motivation, perception of effort and pain
have been associated with decreased run time to fatigue (Carmichael et al., 2005).
Similarly, peripheral fatigue factors originating within the damaged muscle tissue such as
changes in metabolic function have been implicated in the decreased endurance capacity
observed following EIMD (Asp et al., 1998)
In study 3 (Chapter 6), we used 31P-magnetic resonance spectroscopy (31P-MRS) to
evaluate changes in muscle metabolism during dynamic incremental knee extensor exercise
following eccentric exercise. The reduction in time to exhaustion following EIMD was not
associated with an accelerated depletion of [PCr]. Time to exhaustion during the
incremental knee extensor exercise was reduced by 12% following the muscle-damaging
exercise. However the rate of [PCr] depletion was similar in the two experimental
conditions with end exercise [PCr] remaining 13% higher 48 h after the muscle-damaging
exercise. Increases in [Pi] and [Pi]:[PCr] were observed not only at rest but also during
incremental exercise. However, the rate of increase in [Pi] was not altered as a result of the
muscle damage however the premature termination of the test at 48 h resulted in there
being no significant difference in end exercise [Pi] values. It was tempting to speculate that
the limit to exercise tolerance was moderated by [Pi]. However wide inter-subject
variability was observed with the [Pi] values, thus we could not reliably conclude that [Pi]
was, indeed a limiting factor. Rather that end exercise [Pi] may have made an important
contribution to the reduced time to exhaustion experienced following muscle damaging
exercise.

176
8.1.6 Oxygen uptake kinetics and muscle oxygenation
While elevated [Pi] resultant to EIMD may contribute to decrements in performance of
dynamic exercise, microvascular dysfunction observed following EIMD (Kano et al., 2005)
may also contribute to impaired performance due to disruptions to delivery and distribution
of O2 within the capillary bed of the active muscle. We used Near Infrared Spectroscopy
(NIRS) to assess muscle (haemoglobin + myoglobin) oxygenation and to determine the
dynamic balance between oxygen delivery ( Q˙ O2 ) and oxygen uptake ( V˙ O2 )
following the onset of exercise. In particular, the deoxyhaemoglobin (HHb) concentration
([HHb]) NIRS signal was used to non-invasively estimate O2 extraction in the skeletal
muscle microcirculation.
The findings of study 4 (Chapter 7) demonstrated that EIMD resulted in a slowing of
muscle deoxyhaemoglobin concentration [HHb] kinetics without altering pulmonary V˙ O2
kinetics. The observation that the [HHb] kinetics were over 30% slower 48 h after the
performance of eccentric exercise, indicated that there was an increase in the ratio of
oxygen
delivery
to
oxygen
uptake
( Q˙ O2 : V˙ O2 )
during
transitions
to
severe-
intensity
exercise. It was proposed that the elevated Q˙ O2 : V˙ O2
ratio demonstrated by the slower
[HHb] kinetic response (i.e. lower [HHb] at a given V˙ O2 across the exercise transition)
was due to compensatory changes to O2 delivery. In summary, these data indicated that
following EIMD, V˙ O2 kinetics were preserved by compensatory increases in local muscle
blood flow which were able to prevent a measurable slowing of V˙ O2 kinetics.

177
8.2 Limitations
During studies 1 and 4 (Chapters 4 and 7) we employed constant-load, exhaustive exercise
protocols in order to study the human response to dynamic exercise. The use of time or
distance trials such as those employed by Marcora & Bosio (2007) or Twist and Eston
(2009) may provide more ecologically valid models with which to study the effects of
EIMD on the human response to dynamic exercise. However, transitions to constant load
exercise provide the only appropriate platform for modelling of the kinetic response. Thus,
whilst we appreciated the low ecological validity of using exhaustive, constant-load
exercise protocols, we believed we were justified the need to employ our chosen exercise
protocols in order to appropriately examine the human response to dynamic exercise with
and without EIMD.
The relatively small sample sizes used for the investigations that comprise this thesis were
approved as adequate to detect clinically or biologically worthwhile results by the Ethics
Committee of the School of Sport and Health Sciences at the University of Exeter
following appropriate, rigorous power calculations (See Appendix A).
All participants were recreationally active, healthy young men and as such interpretation of
our findings should be restricted to matching populations. Extrapolating findings to other
populations such as highly trained or sedentary groups would be inappropriate. The
protective adaptation to a single bout of eccentric exercise, the ‘repeated bout effect’
(Nosaka & Clarkson, 1995) may last up to 6 months for most symptoms of EIMD (Nosaka
et al., 2001a). Thus the training status of participants may have a profound influence on
their response to dynamic exercise with EIMD.

178
8.3 Implications and future directions
The main findings of the studies that comprise this thesis have implications for the
interpretation of human responses to physical exercise following eccentric exercise. An
awareness of potential changes in metabolic, ventilatory, gas exchange and perceived
exertion responses following eccentric exercise may help coaches, exercise scientists and
health and fitness practitioners to make more informed decisions regarding advice given to
their charges. As has been alluded to earlier in this chapter, the use of constant-load,
exhaustive exercise protocols is not ecologically valid. In future, researchers should seek to
investigate changes in the human response following EIMD using, for example, distance or
time trial protocols, such as those used by Marcora and Bosio (2007) and Twist and Eston
(2009). The increased popularity of high intensity exercise training methods including
resistance training and plyometrics may lead to an increased incidence of EIMD in the active
population. Recreationally active individuals should be aware of the potential alterations to
their performance capacity in the days following this type of training. Future research should
also attempt to elucidate differences in the human response to EIMD between individuals of
different training and activity status.
The influence of eccentric, muscle damaging exercise on the human response to dynamic
exercise has only become the focus of scientific investigation in more recent years (see section
2. 7). Whilst this thesis has extended the examination of some of these responses, many
questions remain unanswered. The various human responses to dynamic exercise evaluated
within this thesis; including ventilatory, gas exchange, perceived exertion and metabolic
responses have only been observed 48 h after EIMD. The use of a discrete observational period
was intentional with the time of 48 h chosen to correspond with the period of maximal muscle

179
soreness. However, future research should attempt to evaluate time-course changes in these
and other human responses during the hours and days following eccentric, muscle damaging
exercise in order to elucidate any potential mechanistic links with time-course changes in
known markers of EIMD such as the loss of force generating capacity.
In studies 3 and 4 (chapters 6 and 7) we used animal studies (Carmichael et al., 2005 and
Kano et al., 2005, chapters 6 and 7 respectively) to inform our understanding and provide
the basis of the research question in human subjects. Understandably, we have not been
able to use some of the techniques employed with animal models. Carmichael et al. (2005)
dissected the brains of eccentrically exercised mice to reveal that increases in inflammatory
cytokine concentrations in the cortex and cerebellum were associated with reduced exercise
tolerance. Inspired by the invasive intravital microscopy studies of rat spinotrapezius
muscle by Kano et al. (2005), we used NIRS to facilitate the non-invasive assessment of
muscle oxygenation following EIMD. In study 4 (chapter 7) we observed a reduced [HHb]
signal in the vastus medialis muscle for a given V˙
O2
at exercise onset 48 h during cycling
after squatting exercise. Future research could extend the use of NIRS to facilitate the non-
invasive assessment of muscle oxygenation following EIMD by examining the response to
a range of different damage and exercise protocols.
8.4 Conclusion
In conclusion, the studies that comprise this thesis have demonstrated how the human
response to dynamic exercise may be altered following exercise-induced muscle damage.
The structural and functional changes that characterise EIMD have been demonstrated to
generate additional or altered ventilatory stimuli during exercise such that the ventilatory

180
response to cycle exercise was elevated at exercise intensities above and below the gas
exchange threshold. Furthermore, the augmented ventilatory response observed has been
shown to result in the gas exchange threshold occurring at a lower work rate without a
concomitant change in the lactate threshold. In combination, these findings demonstrate
that the enhanced ventilation experienced following EIMD may be controlled by additional
or altered neurogenic stimuli rather than changes in metabolic factors. Increases in the
ventilatory response were associated with elevated ratings of perceived exertion (RPE) and
a reduction in time to exhaustion. Differences in minute-by-minute ventilation and RPE
values were eliminated when expressed as a percentage of total exercise duration. These
findings indicate that there is a strong link between the ventilatory and perceived exertion
responses to cycling following EIMD. Although we have shown that an increase in blood
[La] is not an obligatory consequence of EIMD, we have demonstrated, using 31P-MRS,
that muscle metabolic response to dynamic exercise is altered following EIMD. The
accelerated fatigue observed following EIMD may be related either to the increased [Pi]
that was observed at rest and throughout incremental exercise, or to other unmeasured
peripheral or central factors. Finally, we showed that peripheral microvascular dysfunction
resultant to EIMD may contribute to impaired performance due to disruptions to delivery
and distribution of O2 within the capillary bed of the active muscle. Using Near Infrared
Spectroscopy (NIRS) we demonstrated that EIMD resulted in a slowing of muscle
deoxyhaemoglobin concentration [HHb] kinetics without altering pulmonary V˙ O2 kinetics.
Findings demonstrated that there was an increase in the ratio of oxygen delivery to oxygen
uptake ( Q˙ O2 : V˙ O2 ) following EIMD which was due to compensatory changes to
O2 delivery.

