


1
EVALUATING PROTEIN-POLYPHENOL INTERVENTIONS ON SKELETAL
MUSCLE METABOLIC AND FUNCTIONAL ADAPTATIONS TO EXERCISE
Chapter 1 - Literature Review
1.1
Introduction
Skeletal muscle is a highly dynamic tissue providing key mechanical and metabolic
functions essential to human life. Aside from having a critical role in locomotion, skeletal
muscle accounts for approximately 20-30% of energy expenditure at rest (Zurlo, Larson,
Bogardus, & Ravussin, 1990) and is involved in the storage of glucose and lipids in the
postprandial state (Coppack et al., 1990; DeFronzo et al., 1981). Furthermore, skeletal
muscle acts as a principal reservoir for amino acids (Cahill, 1970), comprising ~40%
body mass in individuals aged 18-40 y (Janssen, Heymsfield, Wang, & Ross, 2000).
When required, the breakdown of skeletal muscle provides substrates for hepatic
gluconeogenesis (Felig, 1973) and precursors for the synthesis of various proteins in the
body. Nonetheless, the depletion of skeletal muscle mass is incompatible with life (Keys,
Brožek, Henschel, Mickelsen, & Taylor, 1950) and as such, muscle proteins must be
replaced to maintain muscle homeostasis. Under normal, physiological conditions, daily
rates of synthesis and breakdown in the muscle are approximately equal but various
factors such as injury, exercise and diet influence the rates of each process and the
resultant net protein balance. Upon sustained positive protein balance, caused when rate
of protein synthesis exceeds the rate of protein breakdown, skeletal muscle protein accrual
will occur resulting in hypertrophy (Laurent, Sparrow, & Millward, 1978). Conversely,
when breakdown is greater than synthesis, the resultant negative protein balance will lead
to muscle loss and atrophy (Goldspink, Garlick, & McNurlan, 1983). Manipulating
protein balance to result in protein accrual may enhance injury recovery or adaptations to
exercise. Indeed, strategies targeting muscle protein synthesis specifically have been
demonstrated to accelerate recovery from muscle damage (Davies, Carson, & Jakeman,
2018; Pasiakos, Lieberman, & McLellan, 2014) or enhance muscle mass and strength
following a period of resistance-type exercise training (RET) (Cermak, Res, de Groot,
Saris, & van Loon, 2012; Morton et al., 2018). However, evidence that muscle protein

2
synthesis per se dictates these outcomes is largely circumstantial due to a lack of
interventional studies using direct measures of muscle metabolism.
This chapter will start by giving a historical perspective on the role of myofibrillar
proteins and an overview of the mechanisms regulating protein turnover, before exploring
factors that influence skeletal muscle protein turnover in non-pathophysiological
conditions. The processes that contribute to recovery from muscle damage and
adaptations to resistance exercise will be discussed, highlighting the current
understanding of the role of muscle and myofibrillar protein synthesis. Finally, this
chapter will explore how nutritional interventions can be used to manipulate recovery and
training adaptations, making them a useful tool to further our understanding of the
involvement of myofibrillar protein synthesis.
1.1.1
Contractility of myofibrillar proteins
Myofibrillar proteins comprise ~70% of the total protein content within the muscle (Vann
et al., 2020), with actin and myosin protein filaments directly responsible for contraction
(Huxley & Niedergerke, 1954; Huxley & Hanson, 1954; Huxley, 1953). Knowledge of
these proteins began with a series of works published on the contractility of living and
deceased muscle, where Kühne (1864) detailed the discovery of a coagulating, proteinous
extract from skeletal muscle termed ‘myosin’. This insoluble protein fraction was later
observed to have adenosine triphosphatase activity, which after no ATPase enzyme could
be identified, was attributed to the protein fraction itself (Engelhardt & Ljubimowa,
1939). ‘Myosin’ obtained from rabbit skeletal muscle had divergent properties depending
on the extraction method; the extract from a 20 min process was unchanged following
ATP addition, whereas the extract from a 24 h method contracted ~66% of its original
length (Szent-Györgyi, 1942). This was later attributed to the presence of actin within the

3
myosin extraction, whereas the non-contracting protein was considered to be solely
myosin (Szent-Györgyi, 1942).
High resolution, electron and X-Ray microscopy of both transverse myofibrils (Huxley,
1953) and longitudinal myofibres (Huxley & Niedergerke, 1954; Huxley & Hanson,
1954) revealed the structural arrangement of actin and myosin within contracting fibres.
Striations were observed to comprise of repeating units ~3 µm long, termed sarcomeres,
which changed length from 2.0 – 4.2 µm upon contraction and release (Huxley &
Niedergerke, 1954). A thick band of high electron density (“A band”) within the
sarcomere remained a constant width during muscle contraction. Conversely, bands of
lower electron density both in the centre (“H zone”) and adjacent (“I band”) to the “A
band” were observed to shorten upon contraction (Huxley & Niedergerke, 1954; Huxley
& Hanson, 1954). Transverse imaging identified hexagonal arrangements of thick and/or
thin protein filaments, depending on the band in which the section was imaged (Huxley,
1953), suggesting that these filaments interdigitated to create the characteristic striated
pattern observed during longitudinal microscopy. The thick and thin filaments were
calculated to comprise 5% and 2% respectively of the total wet weight of muscle (Huxley,
1953), agreeing with previous work estimating the ratio of myosin:actin to be 3:1
(Hasselbach & Schneider, 1951). As such, Huxley (1953) proposed that actin and myosin
proteins were the principal components to skeletal muscle contraction.
The tension generated during a contraction is related to the length of the sarcomere
(Walker & Schrodt, 1974). At short lengths (~1.7 μm) actin and myosin filaments are
almost completely overlapping, and so no additional force can be produced upon
contraction stimulus. At 2.5 – 2.8 μm, within the range of normal anatomical movement
(Cutts, 1988), filaments are not completely engaged but partial overlapping allows
enough contact to produce maximum force. However, at long sarcomere lengths (~4.3
μm) there is little-to-no contact between actin and myosin and thus no contractile force
4
can be generated (Walker & Schrodt, 1974). In healthy muscle, titin, a spring-like protein,
extends from the myosin to the Z-disc to prevent complete dis-interdigitation and
maintain normal actin-myosin organisation (Labeit & Kolmerer, 1995).
1.1.2
Overview of muscle protein turnover and signalling
In healthy individuals aged 18-40 years, muscle mass remains relatively stable (Janssen
et al., 2000) due to an equilibrium in muscle protein synthesis (MPS) and breakdown
(MPB). In the postabsorptive state, the net balance of these processes is negative (i.e.
MPS < MPB) (Biolo, Maggi, Williams, Tipton, & Wolfe, 1995b; Phillips, Tipton,
Aarsland, Wolf, & Wolfe, 1997) but becomes positive post prandium (Biolo, Tipton,
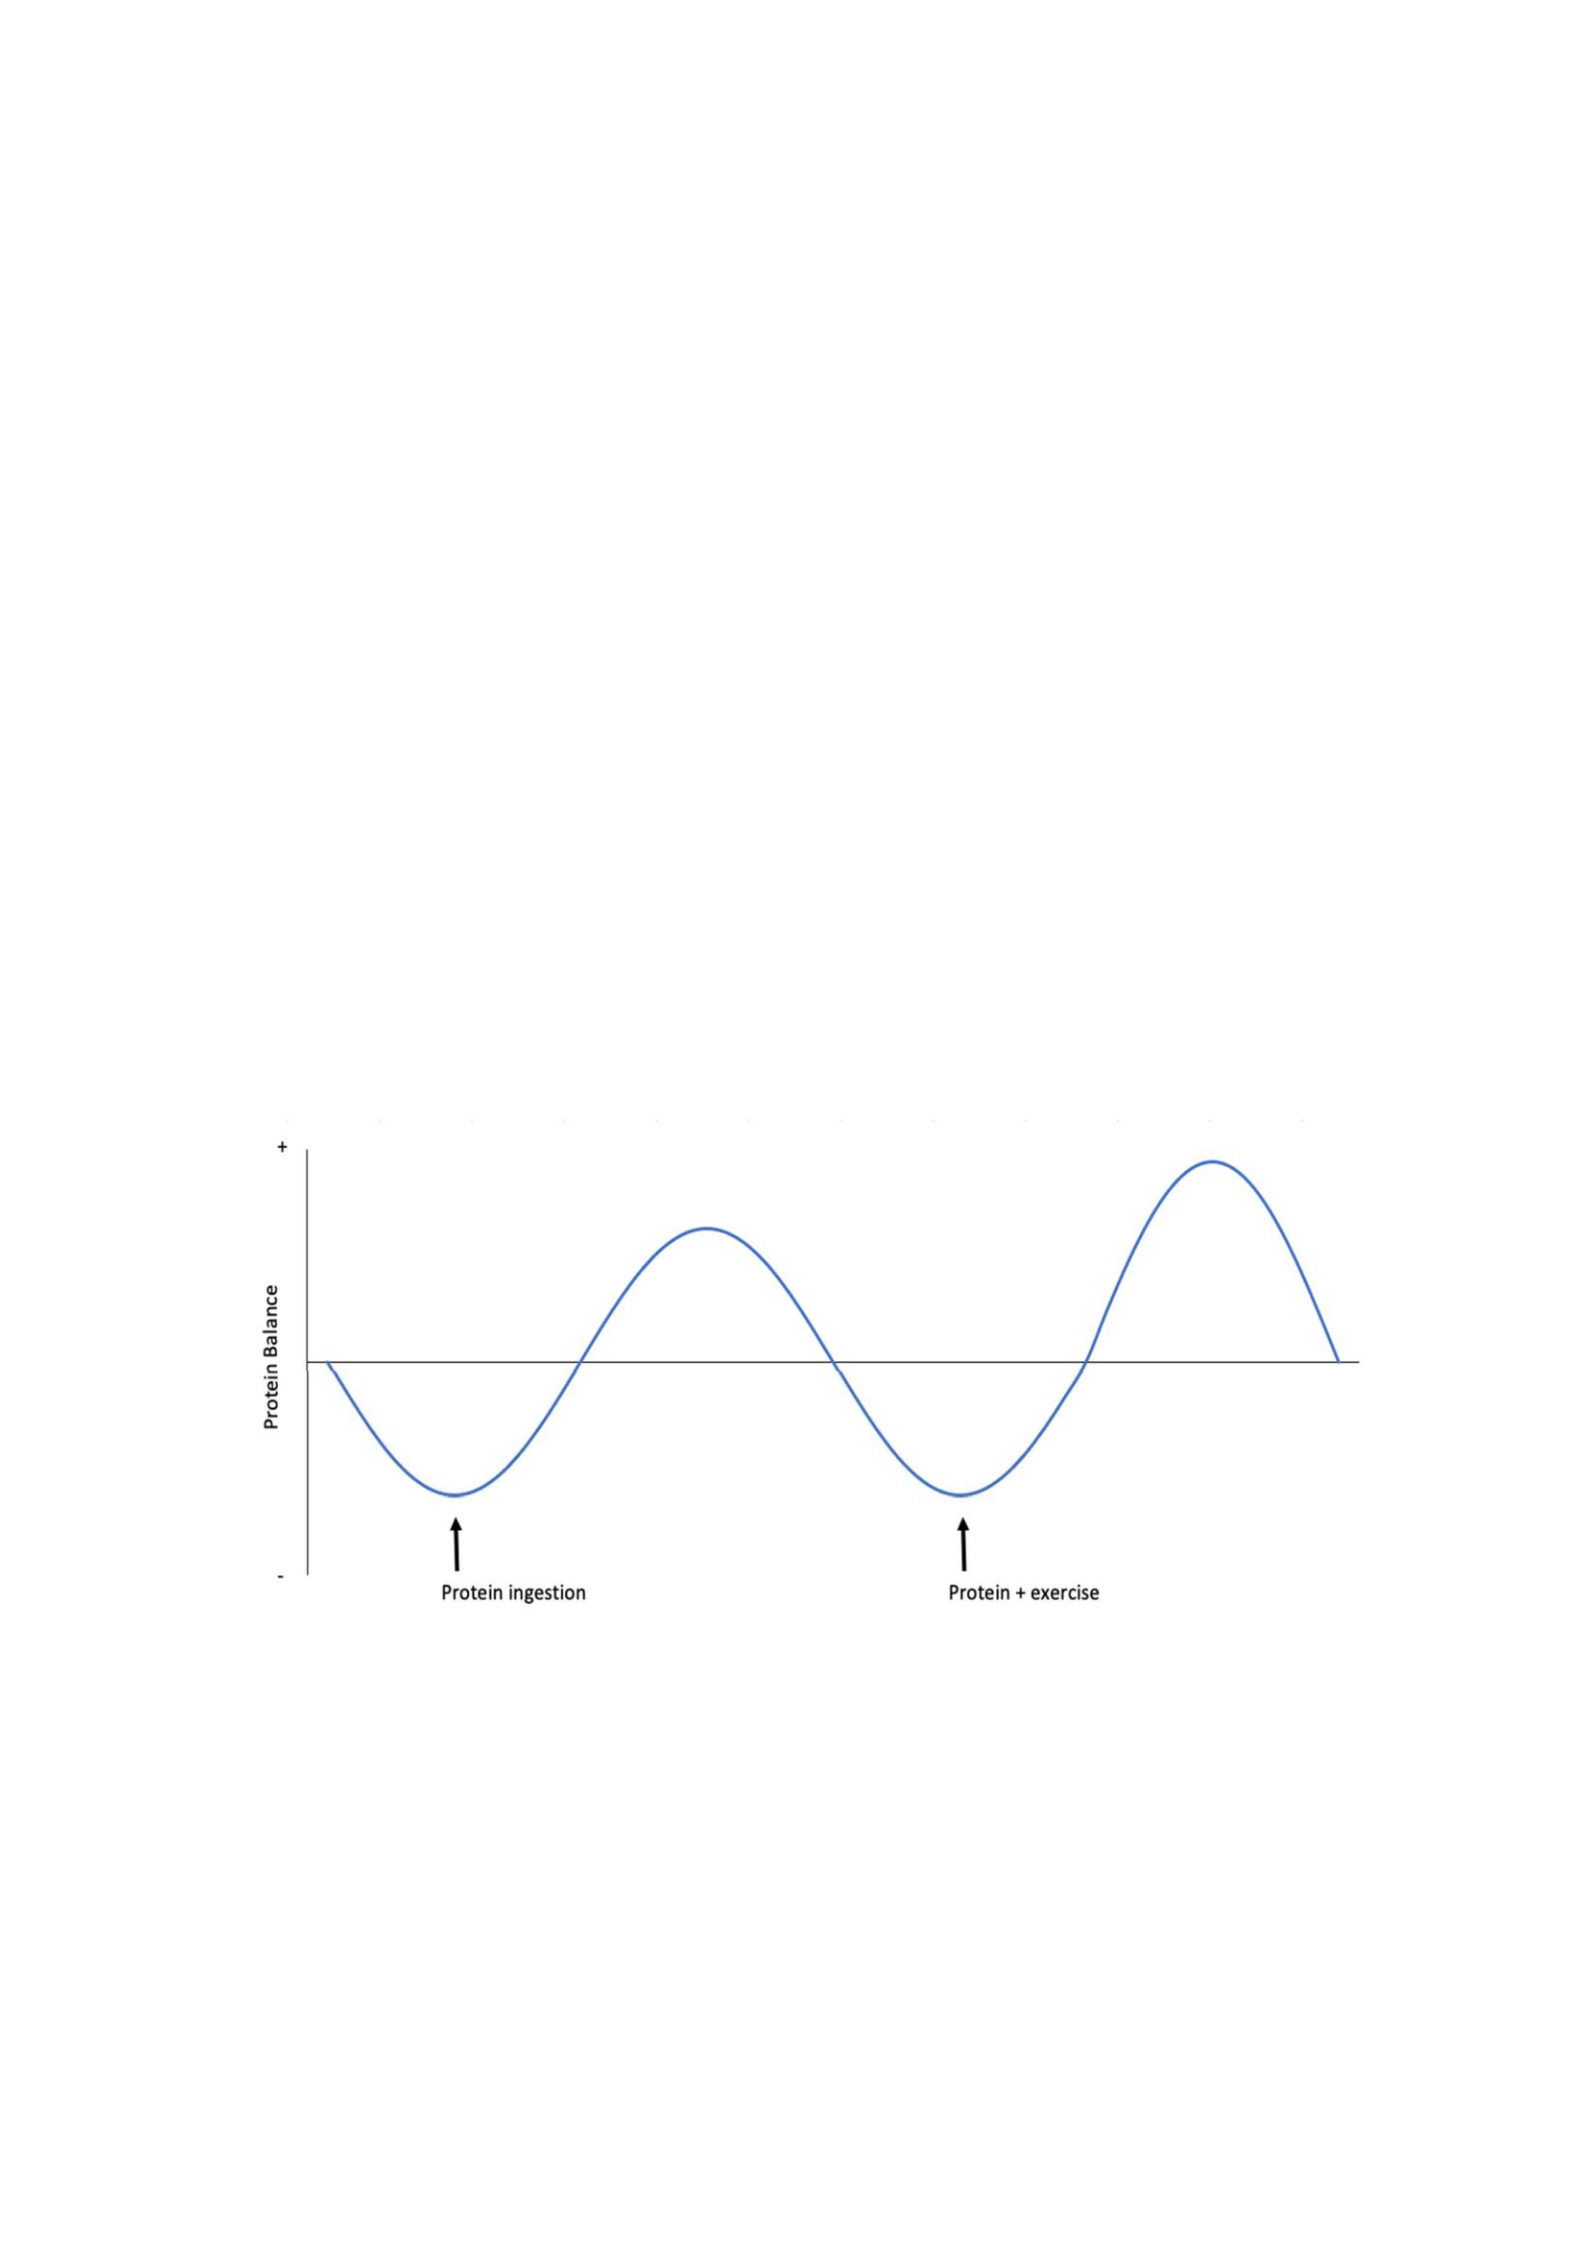
Klein, & Wolfe, 1997) (Figure 1.1). These transient fluctuations transpire into a daily
turnover rate of approximately 1-2%, resulting in steady remodelling over time.
Figure 1.1 Fluctuations in net protein balance in skeletal muscle over time. Net protein
balance is negative in the postabsorptive state but becomes positive after protein
ingestion. Combining exercise with protein intake potentiates this rise, creating greater
positive protein balance.

5
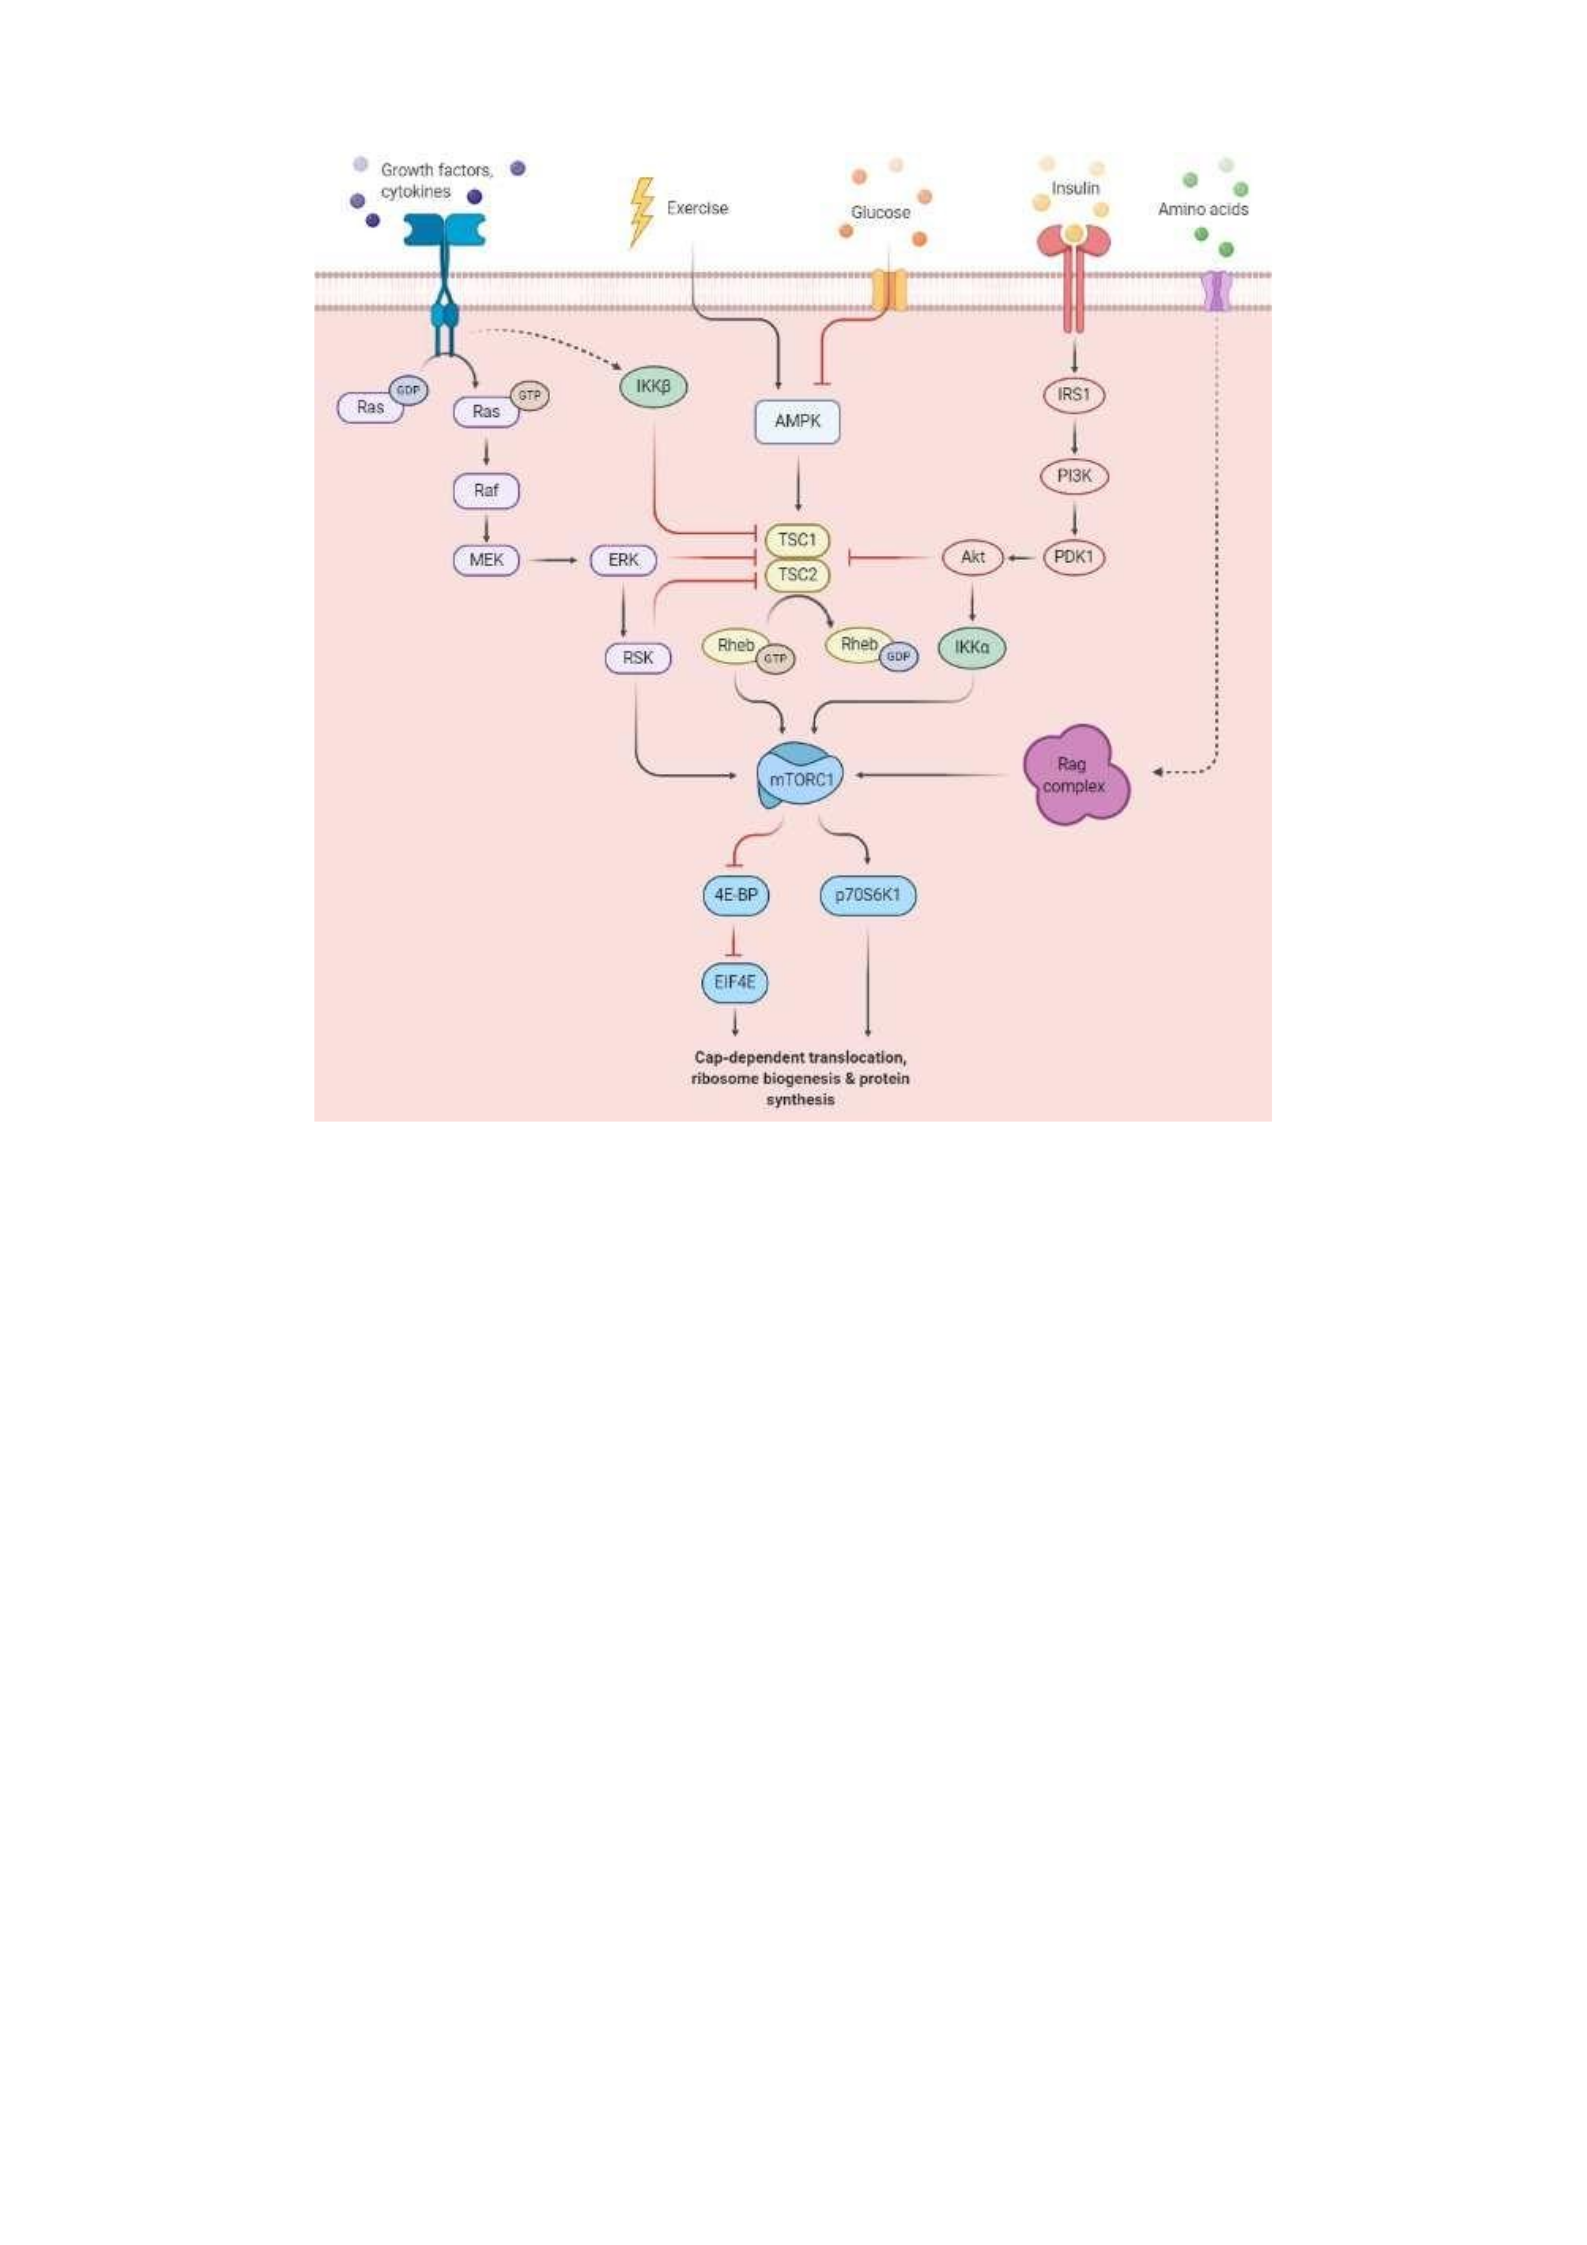
Rates of MPS and MPB are controlled by numerous signalling cascades. Of these, the
mechanistic target of rapamycin complex 1 (mTORC1) is considered a key regulator of
MPS (Figure 1.2). Knowledge of this pathway originated with the identification and
isolation of the antibiotic and antifungal compound rapamycin (Sehgal, Baker, & Vezina,
1975; Vezina, Kudelski, & Sehgal, 1975). Rapamycin inhibits eukaryotic cell growth and
reduces the incorporation of amino acids into intracellular proteins (Singh, Sun, &
Vezina, 1979). In yeast, rapamycin was observed to associate with two serine/threonine
complexes, target-of-rapamycin (TOR) 1 and TOR2, (Heitman, Movva, & Hall, 1991).
Subsequently, a mammalian homologue was identified in the brains of rats (mTOR),
sharing 39% and 43% sequence homology to TOR1 and TOR2, respectively (Sabatini,
Erdjument-Bromage, Lui, Tempst, & Snyder, 1994), suggesting that the mTOR
homologue may be involved in the regulation of cell growth in mammals. Indeed, mTOR
forms two distinct complexes; the growth regulatory effects of rapamycin are mediated
primarily through interactions with mTORC1 (Hara et al., 2002), with mTORC2
unaffected by rapamycin due to the rapamycin-insensitive companion of mTOR
(RICTOR) accessory protein (Sarbassov et al., 2004). Supporting evidence that mTORC1
is involved in growth regulation, downstream proteins are the ribosomal protein S6 kinase
1 (p70S6K1) and eukaryotic initiation factor 4E (EIF4E) binding protein 1 (4E-BP1), that
regulate efficient mRNA translation and progression (Ma & Blenis, 2009). Specifically,
phosphorylation of 4E-BP1 by mTORC1 results in the disassociation from EIF4E,
thereby promoting assembly of the EIF4F complex to enable ribosomal recruitment and
subsequent protein synthesis. Additionally, p70S6K1 appears to phosphorylate further
downstream targets facilitating signal transduction and efficient mRNA translation (Ma
& Blenis, 2009). Under resting, postabsorptive conditions, mTORC1 is predominantly
inactive preventing the phosphorylation of 4E-BP1 and p70S6K1 and thus attenuating
protein synthesis.
6
Figure 1.2. Regulation of mammalian target of rapamycin complex 1 (mTORC1)
signalling via various signalling pathways. Once activated, mTORC1 regulates the
synthesis of proteins within skeletal muscle.
In mammals, activation of mTORC1 is controlled largely by the Ras homolog enriched
in brain (Rheb) protein and the negative regulatory activity of a tuberous sclerosis
complex (TSC) 1 and 2 heterodimer (Ma & Blenis, 2009). At rest, the TSC1-TSC2
heterodimer exhibits GTPase activity rendering the Rheb inactive, preventing stimulation
of mTORC1. Various growth factors and cytokines signal through either the upstream
PI3K-Akt or MEK-ERK signalling cascades. These phosphorylate the TSC1-TSC2
heterodimer and subsequently activate Rheb and mTORC1 to promote protein synthesis.
Activation of mTORC1 in vitro is also independently regulated by the Rag protein family,

7
which promote translocation of mTORC1 to lysosomal membranes where Rheb resides
upon addition of amino acids, thereby promoting mTOR activation (Sancak et al., 2010).
The processes regulating MPB are less well defined but involve three main signalling
pathways: the ubiquitin-proteasome system (UPS), the calpain-calpastatin system and
autophagy. The UPS participates in targeted degradation of misfolded or damaged
proteins in an ATP-dependent manner, regulated by a trio of enzyme classes and the
8.5kDa protein ubiquitin (Kettelhut, Wing, & Goldberg, 1988; Pohl & Dikic, 2019).
Firstly, E1 ubiquitin-activating enzymes bind to and activate ubiquitin in the presence of
ATP, which is subsequently transferred to the E2 ubiquitin-conjugating enzyme. Then,
ubiquitin is conjugated on to the target protein in the presence of an E3 ubiquitin ligase
enzyme, such as muscle RING finger 1 (MuRF1) or muscle atrophy F-box protein
(MAFbx). This process is repeated, whereby subsequent ubiquitin proteins are covalently
attached to form a monomeric or branched ubiquitin chain, which is then recognised by
the 26S proteasome for degradation (Yau & Rape, 2016). Indeed, expression of UPS
components, such as MuRF1 and MAFbx, are upregulated following inflammatory
conditions such as resistance exercise and disuse (Murton, Constantin, & Greenhaff,
2008), as well as being downregulated during physiological insulin infusion with amino
acids (Greenhaff et al., 2008). However, intact myofibrils, which contain multiple protein
structures, are protected from UPS-mediated degradation; in the presence of ATP, UPS-
containing muscle homogenates were observed to release free amino acids when actin,
myosin and troponin proteins were added individually, but not when added as an intact
protein complex (Solomon & Goldberg, 1996). Thus, alternative mechanisms may
explain the clearance of intact proteins.
Skeletal muscle expresses calpain-1, -2 and -3, which are Ca2+ dependent proteases
residing primarily in the cytosol. Following a rise in cytosolic Ca2+ concentration,
calpains are activated, associate with, and cleave numerous
cytoskeletal proteins

8
including the myofibrillar components (Goll, Thompson, Li, Wei, & Cong, 2003).
Calpains are also regulated by the inhibitory binding of calpastatin, which also appears to
require Ca2+ for activity (Kapprell & Goll, 1989). Nonetheless, in the rested state,
cytosolic Ca2+ concentrations are comparatively low and so calpains remain largely
inactive.
The final system regulating MPB is autophagy, which is a lysosomal pathway for the
degradation of non-myofibrillar cytosolic proteins. During mTORC1 inactivity, the
serine/threonine-protein kinase ULK1 induces the formation of a double membrane-
bound vesicle, named the autophagosome (Powers, Morton, Ahn, & Smuder, 2016),
which engulfs intracellular proteins for breakdown. The autophagosome then fuses with
the lysosome, which contains proteases such as cathepsins and releases degraded proteins
and amino acids (Powers et al., 2016). Downregulation of the PI3K-Akt signalling
pathway, which occurs during fasting, results in the upregulation and activation of
forkhead box (FoxO) transcription factors (Stitt et al., 2004). The activation of FoxO3
specifically induces the expression of many autophagy-related genes that are associated
with induction and assembly of the autophagosome, as well as binding to the lysosome
(Zhao et al., 2007). Indeed, FoxO transcription factors also upregulate the expression of
MAFbx and MuRF1 and thus may mediate MPB at rest (Kettelhut et al., 1988; Powers et
al., 2016).
1.2
Factors affecting protein turnover
1.2.1
Exercise
In humans, a single bout of resistance-type exercise provides a potent anabolic stimulus.
Whilst early research using [13C1]-leucine to trace whole-body leucine kinetics indicated
no effect of resistance exercise on whole-body synthesis and breakdown over 2 h

9
(Tarnopolsky et al., 1991), blood flow to the muscle reportedly increases ~75% and rates
of muscle protein synthesis are elevated ~50-129%, reflecting a proportional shift in
amino acid delivery to the muscle (Biolo et al., 1995b; Chesley, MacDougall,
Tarnopolsky, Atkinson, & Smith, 1992; MacDougall, Tarnopolsky, Chesley, & Atkinson,
1992; Phillips et al., 1997; Yarasheski, Smith, Rennie, & Bier, 1992).
Intramuscular RNA content, largely reflective of ribosomal content, is unchanged
following acute resistance exercise, suggesting that MPS stimulation is regulated post-
transcriptionally (Chesley et al., 1992). Indeed, greater post-exercise MPS is matched by
increased mTORSer2448 and p70S6K1Thr389 phosphorylation, with phosphorylation of the
upstream proteins AktSer473 and TSC2Thr1462 up- and down-regulated, respectively, 1 h
post-exercise (Dreyer et al., 2006). Moreover, ERK1/2 phosphorylation at Thr202/Tyr204
is ~8-fold greater immediately post-exercise than at rest or after 1 h, indicating both PI3K-
Akt and MEK-ERK signalling cascades are sensitive to contraction (Dreyer et al., 2006;
Karlsson et al., 2004). Nonetheless, transcriptional regulation in response to resistance
exercise is gene-specific (Murton et al., 2014); for example resistance exercise decreases
expression of DDIT4, an mTOR inhibitor (Gordon, Steiner, Williamson, Lang, &
Kimball, 2016), whilst increasing expression of EIF4E (Monteyne et al., 2020). Thus,
rates of muscle protein synthesis may also be determined at the transcriptional level, with
gene expression inducing the translation of proteins that enable MPS, thereby enhancing
translational capacity.
The acute response to a bout of resistance exercise is influenced by training status
(Chesley et al., 1992; Damas et al., 2016b; Kim, Staron, & Phillips, 2005; MacDougall et
al., 1995; MacDougall et al., 1992; Phillips et al., 2002; Phillips et al., 1997; Phillips,
Tipton, Ferrando, & Wolfe, 1999; Tang, Perco, Moore, Wilkinson, & Phillips, 2008;
Wilkinson et al., 2008). Between 2 – 6 h after a bout of resistance exercise in fed,
untrained individuals, Phillips et al. (2002) observed ~35% greater rates of MPS

10
compared to a rested leg. Following 8 weeks of RET, the exercise-induced difference
between legs was significantly attenuated (~20%, not significantly different to rested leg).
However, these trained individuals exhibited greater maximum strength (Tarnopolsky et
al., 2001). When this is accounted for by prescribing exercise at relative intensities, the
increase in MPS appears greater in trained versus untrained individuals (~162% vs.
~108%) at 4 h. Interestingly, the reverse is true 28 h later (~25% vs. ~70%) (Tang et al.,
2008) suggesting the MPS response is curtailed with training. Consistent with this
suggestion, rates of MPS measured between 12-16 h after resistance exercise were ~28%
greater in an untrained versus trained leg, which although measured when fasted, may
suggest that exercise-induced stimulation of MPS is sustained for roughly twice as long
when untrained (Kim et al., 2005). Nonetheless, should rates of MPS remain constant
over the initial 4 h, which is likely at least in the untrained state (Tang et al., 2008), these
data may reflect greater translational capacity and/or efficiency induced by training.
Indeed, total RNA content and synthesis rates are elevated over 3-6 weeks of RET,
reflecting greater ribosomal biogenesis (Brook et al., 2017; Sieljacks et al., 2019), and
thus may explain these training-induced differences in MPS following acute exercise.
Resistance exercise increases synthesis rates of the myofibrillar protein subfraction
(Cuthbertson et al., 2006; Moore, Phillips, Babraj, Smith, & Rennie, 2005). In the
untrained state, rates of myofibrillar protein synthesis (MyoPS) measured by [2H3]-α-
ketoisocaproic acid infusion increase ~67% from rest over 4 h after acute resistance
exercise, versus ~37% when measured following 10 weeks of RET (Wilkinson et al.,
2008). Interestingly, the absolute rates of MyoPS did not differ post-exercise (~0.103 and
~0.117 %·h-1, untrained and trained, respectively), but were quantitatively greater at rest,
at ~0.086%·h-1 post-training, versus ~0.061 %·h-1 when untrained. Although measured
after feeding, these data are supported by work elsewhere showing ~20% and ~44%
greater postabsorptive MPS and MyoPS in the trained versus untrained state, measured

11
over 3 h with [13C6]-phenylalanine (Reidy et al., 2017). Conversely, when simultaneously
assessing trained and untrained legs following 8 weeks of unilateral RET, Kim et al.
(2005) observed no difference in postabsorptive MyoPS. The reason for these
incongruences aren’t clear but are possibly an artefact of the experimental protocol; tracer
infusions were performed twice by Reidy et al. (2017), pre and post 12 weeks of whole-
body RET, whereas Kim et al. (2005) assessed MyoPS rates between trained and
untrained legs with a single infusion trial. The picture is complicated further when
assessing rates of MyoPS over 48 h using deuterium oxide, which are reportedly ~6%
greater when measured at the start of a 10-week RET program, than when measured after
10 weeks (Damas et al., 2016b). However, given that rates of MyoPS measured over
prolonged periods (i.e., days or weeks) are considered an average of postabsorptive and
postprandial periods, these data would be consistent with a more sustained postprandial
stimulation when untrained, resulting in a greater relative quantity of myofibrillar protein
synthesised over 48 h under free-living conditions, with presumably regular feeding
patterns.
The involvement of muscle protein synthesis in hypertrophy has been understood for
some time, whereby radio-labelled amino acids were observed to be incorporated at
greater rates into hypertrophying muscles of rodents and fowl (Goldberg, 1968; Laurent
et al., 1978). Specifically, the synthesis of myofibrillar proteins appears partly responsible
for resistance-training induced adaptations. Measured over 3 weeks of RET with
deuterium oxide, cumulative MyoPS rates correlate with increases in musculus vastus
lateralis thickness (Brook et al., 2015). Moreover, rates of myofibrillar protein
breakdown, inferred by the change in muscle protein mass and rates of MyoPS, are
unchanged during unilateral RET (8.5 ± 0.6 and 8.1 ± 0.8 g·d-1, trained and untrained
legs, respectively) (Brook et al., 2015). The transition from an untrained to trained
phenotype with regards to MyoPS, as discussed above, may also partly explain the time

12
course of RET adaptations. Over a 6-week unilateral RET intervention in humans, ~68%
1-RM strength and ~77% of m. vastus lateralis thickness gains occurred over the first 3
weeks when rates of MyoPS were greatest, at ~19% greater than between 3 – 6 weeks
(Brook et al., 2015). However, surprisingly, rates of MyoPS captured following the onset
of RET do not correlate with gains in fibre and whole muscle cross-sectional area (Damas
et al., 2016b; Mitchell et al., 2014). Whilst this is an emerging area, the presence of
muscle damage early in training has been hypothesised to explain this discordance
(Damas, Libardi, & Ugrinowitsch, 2018). Indeed, expressing rates of myofibrillar protein
synthesis (MyoPS) relative to the proportion of damaged fibres appears to remove
differences in MyoPS observed between training status (Damas et al., 2016b). This
suggests that rates of MyoPS captured in the untrained state reflect the demand to replace
damaged fibres, rather than contributing to hypertrophy per se. Further supporting this
hypothesis, rates of MyoPS captured after the resolution of muscle damage (~3 weeks),
indicated by the absence of z-line streaming, do correlate with resultant changes in muscle
thickness (Damas et al., 2016b). Nonetheless, this appears to be the only study to date
investigating the reasons for apparent discordance between MyoPS measured following
the onset of RET and resultant hypertrophy, so the role of MyoPS in explaining
adaptations remains unclear.
In contrast to MPS, the effect of exercise on MPB is less well understood. Fewer studies
have used stable isotope methodologies to obtain a dynamic measure of MPB, possibly
due to the limited applicability of using stable isotopes to measure MPB in different
physiological states and the difficulty in obtaining the required samples (Wolfe &
Chinkes, 2005). Nonetheless, early work conducted in untrained individuals showed that
MPB increases by ~31 to ~51% following acute resistance exercise (Biolo et al., 1995b;
Phillips et al., 2002; Phillips et al., 1997; Phillips et al., 1999). Modelling of phenylalanine
kinetics across the artery, vein and muscle indicates that after resistance exercise, a greater

13
proportion of the free amino acids released from breakdown are then reincorporated into
muscle protein, rather than transported out of the cell (Biolo et al., 1995b), explaining
why leg rate of appearance from breakdown appears suppressed with resistance exercise
(Glynn et al., 2010; Reitelseder et al., 2014). As the rise in MPB is smaller both in
magnitude and duration compared to MPS, net balance increases, although in the absence
of amino acid provision will remain negative (Biolo et al., 1995b; Phillips et al., 1997;
Phillips et al., 1999). The exercise-induced increase in MPB appears to be blunted further
in the trained state (Phillips et al., 2002; Phillips et al., 1999). Interestingly, however,
resting MPB is reportedly higher in the trained than the untrained state when fed (~0.082
vs. ~0.065 %·h-1) (Phillips et al., 2002), but when fasted, rates are either equivocal (0.075
and 0.074 %·h-1, trained and untrained respectively) (Phillips et al., 1999), or lower than
when untrained (0.047 vs. 0.066%·h-1, trained vs. untrained respectively) (Reidy et al.,
2017). Nonetheless, very few studies capture breakdown rates and so the response to
training, and subsequent effect on protein turnover, is not fully understood.
1.2.2
Protein ingestion
The effect of feeding on protein synthesis was first described nearly 40 years ago in
humans, where a liquid meal containing ~8 g protein significantly increased whole-body
protein synthesis ~67% and created positive net balance, whilst rates of skeletal muscle
protein synthesis simultaneously increased two-fold (Rennie et al., 1982). Since
publication, many studies have focussed on the effects of protein and/or amino acids
specifically, which routinely and robustly stimulate rates of muscle protein synthesis over
several hours (Bennet, Connacher, Scrimgeour, Smith, & Rennie, 1989; Biolo et al.,
1997; Paddon-Jones et al., 2004; Volpi, Mittendorfer, Wolf, & Wolfe, 1999).
Specifically, data from arterio-venous balance and 3-pool modelling of amino acid

14
kinetics indicate that exogenous amino acids primarily stimulate protein synthesis,
whereas protein breakdown is less or not affected (Miller, Tipton, Chinkes, Wolf, &
Wolfe, 2003; Rasmussen, Tipton, Miller, Wolf, & Wolfe, 2000; Tipton, Ferrando,
Phillips, Doyle, & Wolfe, 1999).
Following ingestion, several regulatory steps contribute to elevating amino acid
availability for protein synthesis. Digestion speed and gastric emptying represent the first
of these; for example, rate of exogenous phenylalanine appearance is ~27% greater over
6 h after ingestion of 35 g casein hydrolysate versus intact casein (Koopman et al., 2009).
Furthermore, sitting upright to increase gastric emptying after consuming 20 g protein
results in greater peak plasma leucine concentration versus lying supine (~213 versus
~193 μmol·L-1) (Holwerda, Lenaerts, Bierau, Wodzig, & van Loon, 2017). Protein
ingestion causes insulinaemia, which elevates blood flow and nutrient delivery to the
skeletal muscles (Fujita, Rasmussen, Cadenas, Grady, & Volpi, 2006; Fukagawa,
Minaker, Young, & Rowe, 1986; Gelfand & Barrett, 1987; Timmerman et al., 2010).
Pharmacologically inhibiting blood flow such that amino acid delivery is similar to rest
reduces the stimulatory effect of insulin on MPS by half (Timmerman et al., 2010).
Moreover, cold-water immersion lowers MPS post-exercise ~20% (Fuchs et al., 2020)
highlighting the role of blood flow in amino acid delivery. Insulin infusion at 30 mU·L-1
reportedly halves phenylalanine release from the muscle into circulation, which coincides
with a ~60% reduction in MAFbx protein content versus basal, suggesting suppressed
protein breakdown (Greenhaff et al., 2008). Following delivery, amino acids are then
transported into muscles through membrane-bound transporters, increasing intramuscular
amino acid availability (Bergstrom, Furst, & Vinnars, 1990; Bohe, Low, Wolfe, &
Rennie, 2003; Dickinson, Drummond, Coben, Volpi, & Rasmussen, 2013). Moreover,
essential amino acids increase the expression of solute-linked carriers (SLC)7A5,
SLC38A2, SLC7A1 and SLC36A1 ~3-fold following resistance exercise (Dickinson et al.,

15
2013). In vivo, the presence of amino acids within the cell enables Rag-Ragulator-
mediated translocation of mTORC1 to the lysosomal surface, promoting interaction with
Rheb (Figure 1.2) (Sancak et al., 2010). Leucine appears key to stimulate MPS (Buse &
Reid, 1975; Churchward-Venne et al., 2012) as pronounced mTORSer2448 phosphorylation
and phosphorylation of the downstream effectors 4EBP1Thr37/46, p70S6K1Thr389 and
rps6Ser235/236 occur with administration of leucine to C2C12 myocytes (Atherton, Smith,
Etheridge, Rankin, & Rennie, 2010b). In humans, leucine and/or other branched-chain
amino acids stimulate MPS and mTORSer2448 phosphorylation, as well as enhancing
p70S6K1 phosphorylation at Ser424/Thr421 and Thr389 (Churchward-Venne et al., 2012;
Karlsson et al., 2004). Notably, signalling through this pathway is not strictly reflective
of MPS, as 25 g whey sustains the rise in MPS beyond 2-3 h, despite similar Akt and
mTOR phosphorylation compared to 6 g whey with added leucine or essential amino acid
blends (Churchward-Venne et al., 2012). As such, these data suggest that once stimulated,
availability of all amino acids are required to maintain protein synthesis (Churchward-
Venne et al., 2012; Fuchs et al., 2019).
1.2.3
Exercise plus protein ingestion
In the absence of nutrition, net protein balance remains negative after exercise with
breakdown contributing ~55% of amino acids used for synthesis (Biolo et al., 1995b;
Phillips et al., 1997; Phillips et al., 1999). However, protein provision following
resistance exercise creates net positive protein balance, which appears to be driven
through greater amino acid delivery and inward transport, and subsequent rise in MPS,
rather than reductions in MPB per se (Biolo et al., 1997; Rasmussen et al., 2000; Tipton
et al., 1999). In support of this, signalling through the mTOR pathway was greater when
~21 g amino acids were provided following exercise, with ~2-fold greater rates of MPS

16
and AktSer473, mTORSer2448 and p70S6K1Thr389 phosphorylation compared to fasting
(Dreyer et al., 2008). Moreover, protein ingestion following exercise induces a more
pronounced increase in MPS, sustained for ~5-6 h, versus ~3h at rest (Churchward-Venne
et al., 2012; Moore et al., 2009b; Pennings et al., 2011b), suggesting that contraction
sensitises the muscle to protein ingestion. This may be volume-dependent, as a ~28%
greater rise in MyoPS was observed following three sets versus one set of resistance-type
exercise in knee extensor muscles (Burd et al., 2010a). Furthermore, this sensitisation was
maintained 24 h later, whereby 20 g whey protein stimulated rates of MyoPS and
p70S6K1Thr389 phosphorylation ~2-fold only in the group that performed the greater
volume of resistance exercise (Burd et al., 2010a).
The protein synthetic response can be optimised further with respect to protein quantity
and timing. Moore et al. (2009a) described how muscle protein synthesis increased in a
dose-dependent manner after the consumption of up to 20 g egg protein following
resistance exercise. Although only one dose was consumed above this (40 g), MPS was
not stimulated further; instead, rates of leucine oxidation tended to be greater (~18%
increase, compared to 20 g), suggesting that 20 g protein is the optimal quantity for
stimulating rates of MPS (Moore et al., 2009a). These findings were later replicated
investigating the protein synthetic response of the myofibrillar subfraction, whereby rates
of MyoPS were similar (~0.073%·h-1) in trained individuals consuming either 20 or 40 g
whey protein following resistance exercise (Witard et al., 2014). At a similar time, an
investigation into the optimal pattern of daily protein intake with regards to maximising
post-exercise MPS over 12 h was performed (Areta et al., 2013). The stimulatory effect
of 80 g dietary protein was ~31 – 48% greater when consumed as 20 g every 3 h, versus
both 40 g every 6 h or 10 g every 1.5 h (Areta et al., 2013). Thus, it appears that 20 g
dairy or egg protein provides an optimal stimulus to promote mixed muscle and
myofibrillar protein synthesis. However, importantly, the results by Moore et al. (2009a),

17
Areta et al. (2013) and Witard et al. (2014) were obtained from participants with body
mass between ~82 – 86 kg performing leg-only exercise. Given that amino acid delivery
and uptake is increased in exercising muscle (Biolo et al., 1995b; Biolo et al., 1997), it
stands to reason that a greater mass of skeletal muscle requires more exogenous amino
acids to maintain similar levels of delivery. Supporting this suggestion, rates of MyoPS
when fed 20 and 40 g of whey protein were observed to be ~29% and ~24% lower after
whole-body exercise than in a previous study using single-leg exercise (Macnaughton et
al., 2016; Witard et al., 2014). Additionally, in contrast to the aforementioned dose-
response studies, MyoPS rates in the 40 g condition were significantly (~20%) greater
than with 20 g (Macnaughton et al., 2016). However, an analysis of 23 experimental
groups from 13 studies was subsequently performed, revealing that activated muscle mass
is unrelated to the dose of protein required to maximally stimulate MyoPS, and instead is
best described when corrected for body mass at 0.31 ± 0.08 g·kg-1 (Moore, 2019).
Therefore, the ability to detect further stimulation with 40 g was likely due to enhanced
statistical power afforded by the 30 participants included in the analysis (Macnaughton et
al., 2016).
Given that protein in combination with resistance exercise creates net positive protein
balance in the acute setting, several studies have used protein supplementation as a tool
to further manipulate gains in skeletal muscle strength and hypertrophy over a prolonged
(>6 weeks) period of resistance training. Meta-analyses of available literature reveal that
greater daily protein intakes further augment gains in muscle strength, lean body mass
and muscle fibre size with prolonged (>6 weeks) resistance training (Cermak et al., 2012;
Morton et al., 2018). Discrepant findings may be explained by shorter training duration
(~4 weeks), as 1-RM and isometric maximum voluntary contraction (MVC) gains are not
further potentiated with 21 g protein (Boone, Stout, Beyer, Fukuda, & Hoffman, 2015) or
30 g amino acids (Lemon, Tarnopolsky, MacDougall, & Atkinson, 1992) over this time.

18
Given that protein ingestion explains ~9% of the total improvement in 1-RM strength
during >6 weeks of RET (Morton et al., 2018), and that rapid neurological adaptations
are prominent in the first 2-3 weeks of training (Hakkinen et al., 1998; Seynnes, de Boer,
& Narici, 2007), strength gains are evidently multifactorial. Indeed, gains in muscle
strength are proposed to be determined predominantly by the practice of that task
(Buckner et al., 2019; Dankel et al., 2020). Illustrating this point, Dankel et al. (2020)
observed how gains in 1-RM strength were similar between groups performing 1-RM
training only and performing a typical RET program (i.e., 4 sets of 8 – 12 repetitions at
100% 8-12RM), versus time-matched, non-exercised controls. However, neither group
improved maximal isokinetic peak torque. Interestingly, the standard deviation was
approximately 2-fold greater in the traditional training group, whereas those who trained
in 1-RM were no more variable than that the untrained cohort (i.e., variability ascribed to
random error). Thus, it appears that muscle strength measurements with training are
dependent on the similarity of the measurement to the manner of training (Buckner et al.,
2017). Taking these observations into consideration, the influence of protein on measures
of muscle strength may only be detectable if the training duration is long enough (> 6
weeks), and if regular practice of that task is performed.
1.3
Muscle damage from unaccustomed exercise
1.3.1
Physiology of damage
Muscle damage can be induced experimentally through various methods, either
mechanically such as freeze-injury, crush, or strain or pharmacologically such as barium
chloride, cardiotoxin or notexin application. In humans, mechanically-induced muscle
damage is a commonly experienced phenomenon, occurring as a result of unaccustomed
loading to the muscle during daily living (Yilmaz, Orgenc, Ergenc, & Erkan, 2008) and

19
sporting activities (Gibala, MacDougall, Tarnopolsky, Stauber, & Elorriaga, 1995;
Neubauer, Konig, & Wagner, 2008). Thus, understanding the mechanisms that dictate
recovery from muscle damage is relevant for a large proportion of the population.
However, such mechanistic understanding is often derived from rodent studies where
experimental models induce severe damage and necrosis in the muscle tissue followed by
full myofiber regeneration (Hardy et al., 2016). Inducing severe muscle damage in a
controlled manner in humans is both impractical and unethical, and instead, maximal
voluntary lengthening contractions are often used. In these situations, severe damage or
muscle tears are uncommon and necrosis rarely encountered (Grounds, 2014). For
example, no evidence of myofiber necrosis was observed after 210 maximal voluntary
eccentric contractions, whereas the same quantity of electrically stimulated contractions
in the contralateral leg reduced desmin protein content and increased the presence of
CD68+ reactive macrophages within the muscle fibre, indicative of necrosis (Crameri et
al., 2007). Furthermore, in muscle biopsy samples from m. gastrocnemius collected
immediately after a 160 km downhill ultramarathon race, <1% of 3698 fibres analysed
were necrotic (Crenshaw, Friden, Hargens, Lang, & Thornell, 1993). Therefore, it would
appear that myofiber regeneration is rarely required. Indeed, ~69% of sporting injuries
resolve within 7 days (Edouard, Branco, & Alonso, 2016), as do damage markers
following voluntary exercise models of damage in humans (see 1.3.2 Markers of muscle
damage; Figure 1.3), whereas severe injury in rodents impairs muscle function and causes
regenerative and inflammatory events in the muscle beyond 28 days (Hardy et al., 2016;
Winkler et al., 2011). Rather, the metabolic response following damage-inducing,
voluntary exercise likely reflects remodelling and repair rather than full myofiber
degradation and regeneration (Grounds, 2014; Yu, Carlsson, & Thornell, 2004) and so
translation of animal models of severe damage to human models of voluntary exercise is
limited. Unless otherwise specified, muscle damage and injury as described hereafter in

20
this thesis refers to situations of moderate damage expected to induce muscle
remodelling, rather than myofiber regeneration.
During a lengthening, or eccentric muscle contraction, external forces overcome the
intrinsic contractile force produced by the myofibrils, causing the muscle to lengthen. As
the muscle is absorbing work rather than producing it, the maximum force produced
during an eccentric contraction exceeds that produced during a concentric contraction by
~20% (Beltman, Sargeant, van Mechelen, & de Haan, 2004). However, eccentric
contractions induce greater damage to the muscle than concentric contractions, even when
matched for workload (Newham, McPhail, Mills, & Edwards, 1983a; Newham, Mills,
Quigley, & Edwards, 1983b; Vissing, Overgaard, Nedergaard, Fredsted, & Schjerling,
2008). This observation is explained by the “popping sarcomere” theory, which proposes
that during an eccentric contraction the weakest sarcomeres extend to a point of no
overlap between actin and myosin proteins (Morgan, 1990). At this point, the supporting
myofibrillar proteins, such as titin, provide passive tension but are not able to generate
active force. Additionally, myofibrillar structures may become temporarily damaged and
unable to contract (Friden, Sjostrom, & Ekblom, 1983; Newham et al., 1983a). Sarcomere
stretching also transmits lateral force to the sarcoplasmic membrane via the costameres
(Hughes, Wallace, & Baar, 2015), which may disrupt membrane integrity and calcium
ion homeostasis. As a consequence of the inability to propagate an action potential,
muscle contraction is impaired and free calcium ions can activate calpain-calpastatin
pathways of MPB (Warren et al., 1993).
1.3.2
Markers of muscle damage
Longitudinal forces that are transmitted along the disrupted sarcomere cause the Z-discs
to become over-stretched and damaged. Using microscopy, this can be observed, and

21
damage quantified by assessing the loss to the typical striated pattern produced by
myofibrillar protein structures (Friden et al., 1983; Newham et al., 1983a). Indeed, greater
Z-disc disruption is observed after eccentric versus concentric exercise in individuals
naïve to resistance exercise (Gibala et al., 1995; Newham et al., 1983a; Raastad et al.,
2010) and in some cases, Z-disc disruption has been demonstrated to correlate with loss
of contractile force at a given time point post-eccentric exercise (Raastad et al., 2010).
Although Z-disc disruption is evident immediately post-eccentric exercise, peak
disruption may occur after 1-4 days (Friden et al., 1983; Newham et al., 1983a; Raastad
et al., 2010; Yu et al., 2004). Accordingly, whether this marker reflects the extent of
muscle damage is disputed. In a series of early studies, Newham et al. (1983b) described
how eccentric bench stepping exercise caused an immediate and profound loss of
maximal voluntary contractile force, which was accompanied by a greater prevalence of
disrupted myofibers assessed by electron microscopy (Newham et al., 1983a). However,
contractile force improved after 24 h, whereas disrupted myofibers were more numerous
than when measured immediately after exercise (Newham et al., 1983a; Newham et al.,
1983b). Due to the non-uniform nature in which sarcomeres are disrupted, muscle biopsy
sampling in humans may not be reflective of the full extent of muscle damage (Raastad
et al., 2010) thus the aforementioned results may be due to random sampling. However,
physiological mechanisms may also explain the discrepancy between functional recovery
and appearance of damage. Indeed, the time course of myofibre disruption appears to
correlate more with leukocyte infiltration and the remodelling of myofibrillar proteins,
rather than loss of contractile force per se (Lowe, Warren, Ingalls, Boorstein, &
Armstrong, 1995). Specifically, disturbances in the sarcomere that are considered to be
disrupted and elongated Z-discs stain strongly for actin and desmin proteins, whilst
staining for the Z-disc protein α-actinin is lost (Yu et al., 2004). Thus Z-disc disruptions
22
may be more reflective of remodelling, particularly the synthesis of actin and desmin and
breakdown of α-actinin.
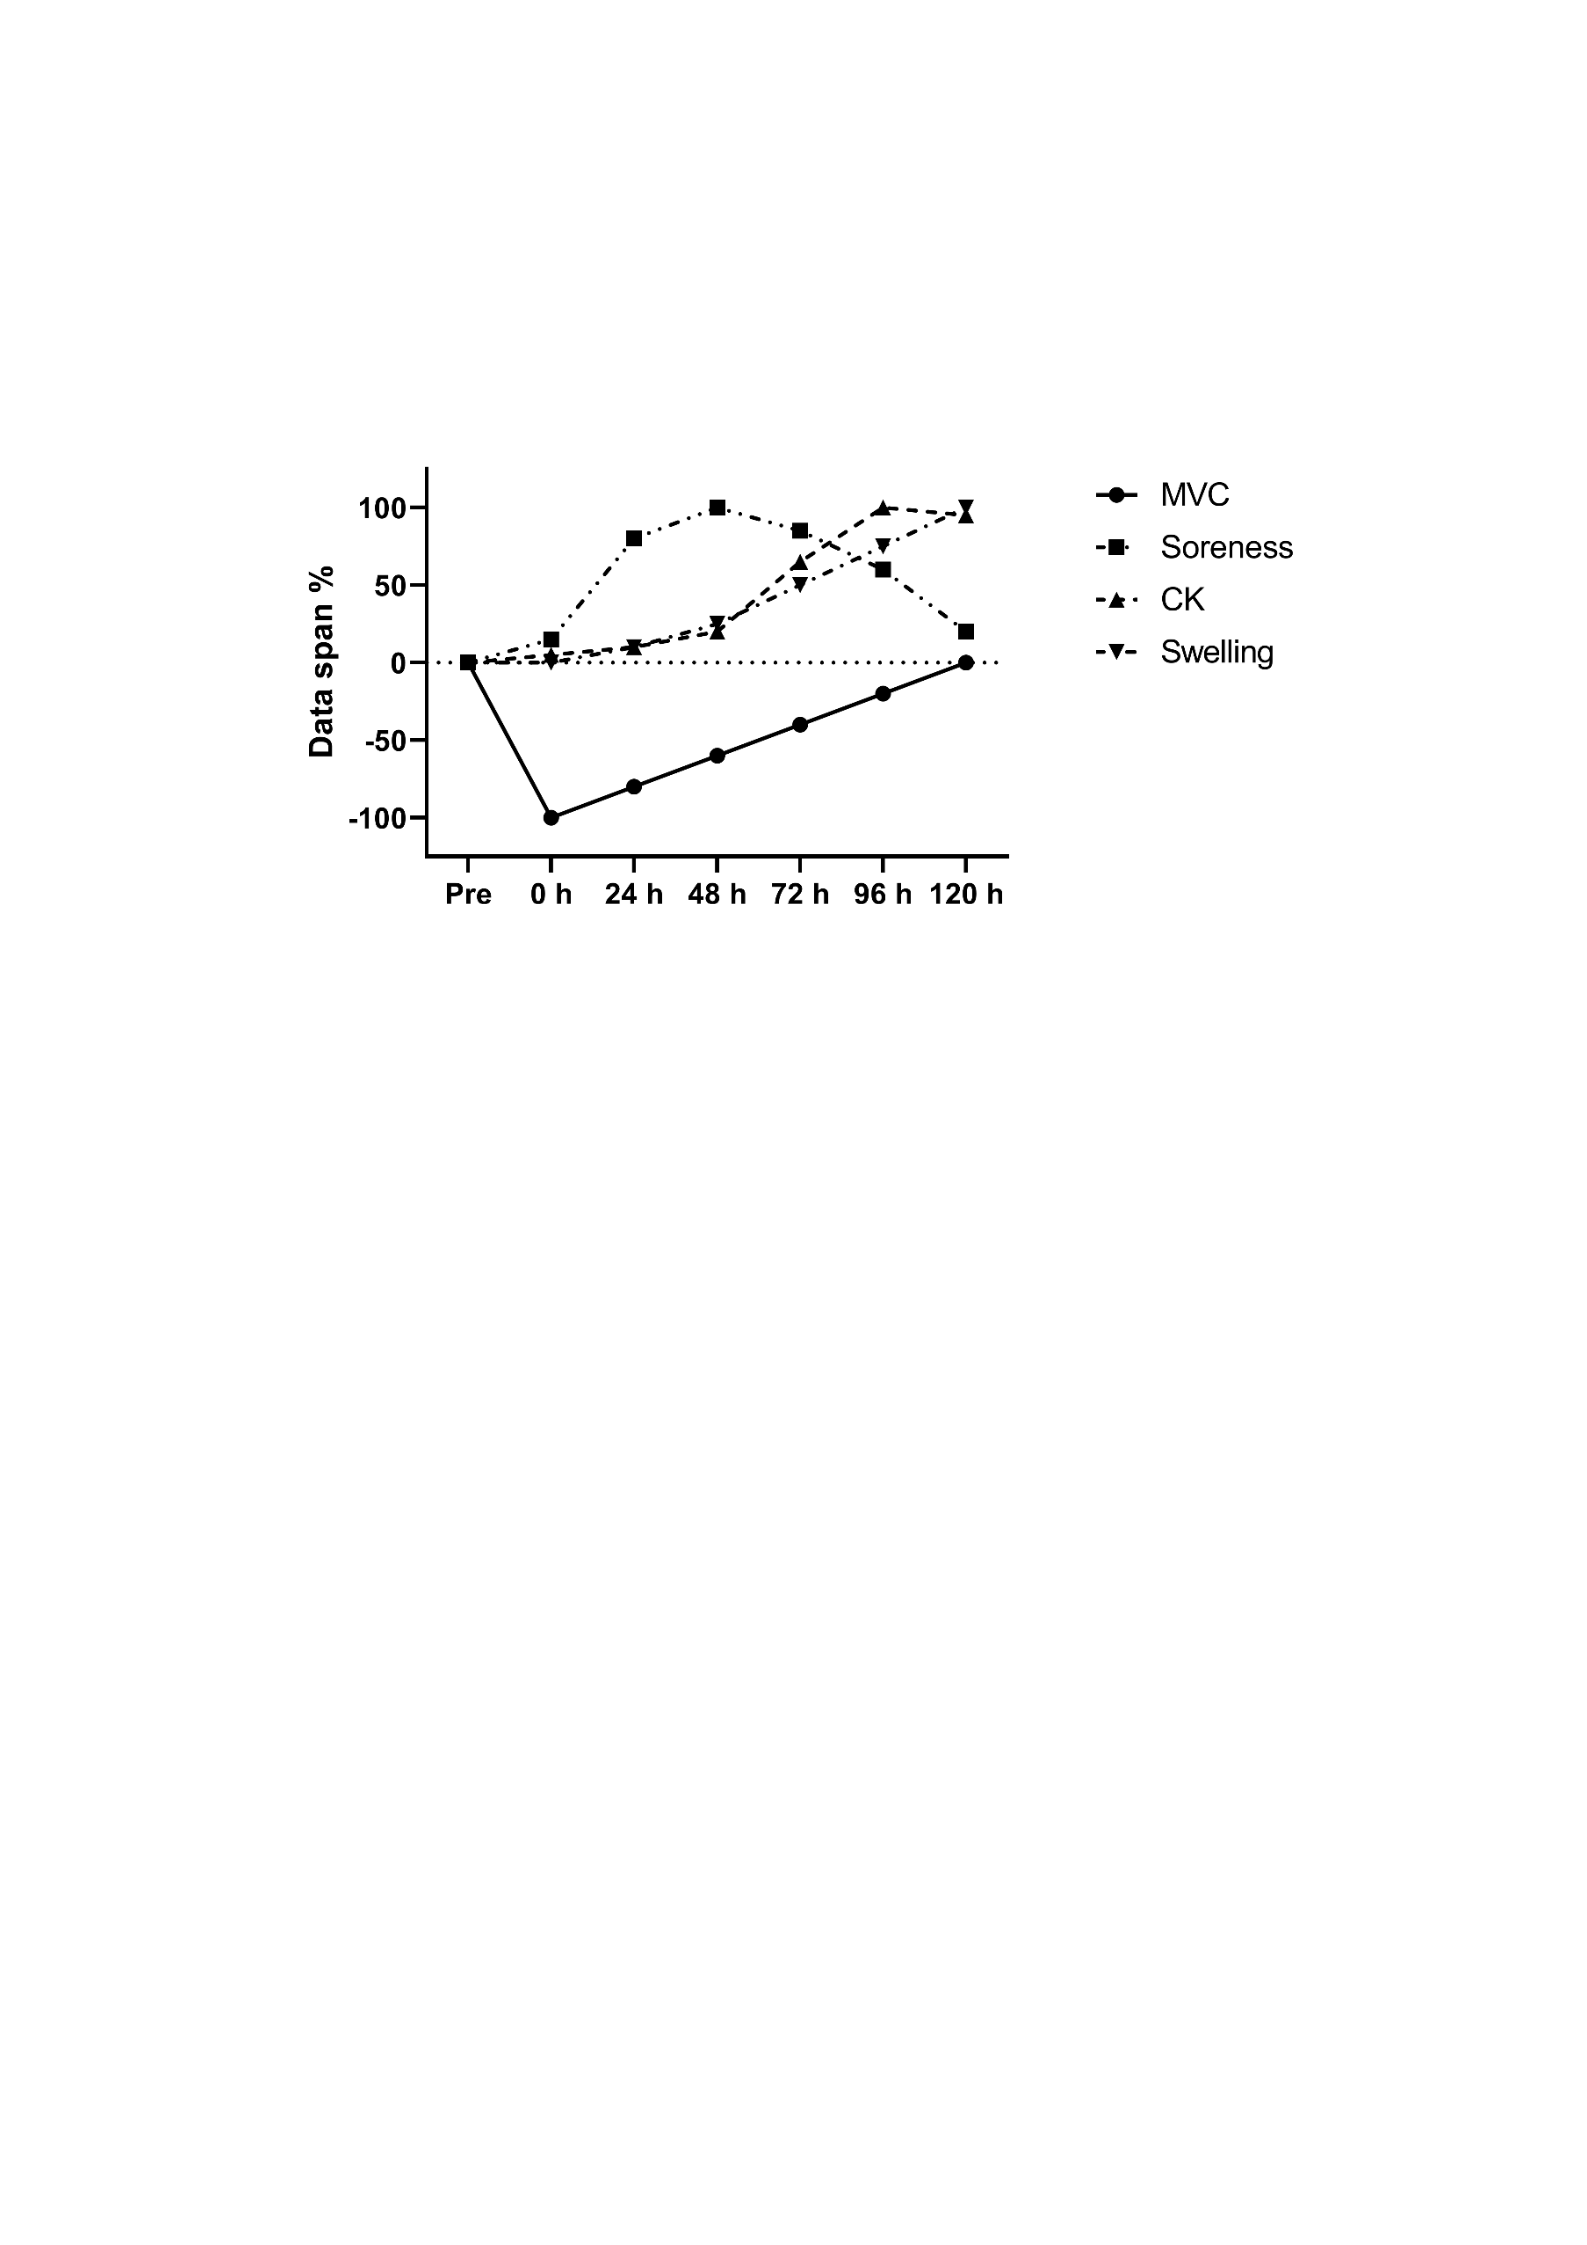
Figure 1.3. Model data representing the time course of changes in maximal voluntary
contraction (MVC), muscle soreness, creatine kinase (CK) activity in blood and muscle
swelling assessed before (Pre), immediately after (0 h), and every 24 h up to 120 h after
maximal eccentric muscle contractions. Data normalised to pre-exercise values and the
greatest magnitude of change in positive and negative directions. Data are derived from
previously published reviews and large-scale analyses (Clarkson & Hubal, 2002; Damas,
Nosaka, Libardi, Chen, & Ugrinowitsch, 2016a).
Other markers of damage have been studied extensively and described in detail (Clarkson
& Hubal, 2002; Malm, 2001; Nosaka, Lavender, Newton, & Sacco, 2003; Proske &
Morgan, 2001; Warren, Lowe, & Armstrong, 1999). One of the earliest studies to make
reference to indirect markers of muscle damage described the soreness experienced by an
untrained muscle after contracting against a strong spring (Hough, 1902). Since
publication, multiple symptoms of muscle damage have been identified, although they
resolve over different time-courses (Figure 1.3). For example, a substantial loss of torque,

23
considered the most reliable indirect measure of muscle damage (Warren et al., 1999),
appears immediately and may persist for several days post-exercise (Farup et al., 2014a;
Vissing et al., 2008). Conversely, soreness has consistently been shown to peak 24 – 48
h following damaging exercise (Legault, Bagnall, & Kimmerly, 2015; Rankin, Stevenson,
& Cockburn, 2015; Vissing et al., 2008), despite being largely unchanged immediately
post-exercise. Finally, blood-borne markers of muscle damage such as creatine kinase
(CK) may increase significantly 3 to 4 days after the initial damaging bout (Nosaka &
Clarkson, 1992; Vissing et al., 2008), depending on the protocol used, which coincides
with oedema in the damaged muscle (Mair et al., 1992).
1.3.3
Factors influencing the extent of muscle damage
Contraction force influences extent of muscle damage, with sub-maximal exercise
modalities, such as bench-stepping or downhill running, typically reporting ~15-25% loss
of MVC strength post-exercise (Baumann et al., 2014; Eston, Lemmey, McHugh, Byrne,
& Walsh, 2000; Green et al., 2010). Conversely, eccentric contractions performed at
maximum intensity induce greater loss of MVC strength (Nosaka & Newton, 2002), with
losses greater than 25% commonly shown (Buckley et al., 2010; Farup et al., 2014a;
Hicks, Onambele, Winwood, & Morse, 2016). In particular high-force eccentric
contractions appear to induce a greater degree of muscle damage than work-matched
contractions performed at low-force (Paschalis, Koutedakis, Jamurtas, Mougios, &
Baltzopoulos, 2005), indicating that the extent of damage is related to the volume of
eccentric exercise performed at high contraction intensity.
Previous exposure to muscle damage produces a robust protective effect on the muscle
from subsequent damaging bouts. Following 30 min of downhill running (-10 degrees
slope), leg muscle soreness, serum CK activity and myoglobin concentration were

24
significantly attenuated when bouts were repeated after 3 and 6, but not 9, weeks (Byrnes
et al., 1985). After maximal eccentric contractions of the elbow flexors, this protective
effect persisted when bouts were separated by over 6 months (Nosaka, Sakamoto,
Newton, & Sacco, 2001). In addition, previous muscle damage in one limb may protect
the contralateral limb from subsequent bouts, although this effect appears less pronounced
and may only last ~4 weeks (Chen, Chen, Lin, Yu, & Nosaka, 2016). The mechanisms
underpinning this contralateral effect are unclear. However, when two bouts of 100
eccentric contractions of knee extensors were separated by 4 weeks, the rise in NFκB
DNA-binding activity was attenuated in the contralateral limb after the second bout (123
± 3%, versus 109 ± 3%), suggesting possible suppression of inflammation. However,
repeated exposure to eccentric exercise induces greater accumulation of heat-shock
protein (HSP)27, HSP70 and αB-crystallin in myofibrillar structures, protecting against
further damage (Paulsen et al., 2009). Although this was observed in the ipsilateral limb,
dampened inflammation could be a result, rather than a cause, of the contralateral repeated
bout effect. Regardless of the mechanisms, together, these observations have important
consequences for study designs; in eccentric exercise models, parallel study designs may
be preferred to crossover when investigating interventions to mitigate muscle damage.
1.3.4
Muscle damage and inflammation
Exercise-induced muscle damage induces a robust inflammatory response, which in non-
pathophysiological conditions is a tightly coordinated process dictating recovery and
return to homeostasis (Chazaud, 2016; Peake, Neubauer, Della Gatta, & Nosaka, 2017).
Leukocytes, particularly neutrophils, begin to accumulate in the hours after eccentric
exercise and are present in damaged muscle tissue for roughly 24 h (Peake, Nosaka, &
Suzuki, 2005; Peake et al., 2017). Histological staining suggests monocytes and

25
macrophages also accumulate over this time and are likely the predominant leukocyte
present between 24 – 168 h after maximal eccentric exercise (Paulsen et al., 2010).
Neutrophils and monocytes break down damaged tissue through phagocytosis and the
release of proteolytic enzymes and reactive oxygen and nitrogen species (Nathan, 2006).
These cells also release proinflammatory cytokines including tumour necrosis factor
(TNF)-α and interleukin (IL)-6, serving to propagate the inflammatory response during
recovery (Chazaud, 2016). The presence of macrophages within skeletal muscle has been
verified in humans after ultra-endurance (Marklund et al., 2013) and maximal voluntary
eccentric exercise (Paulsen et al., 2010; Paulsen et al., 2013). Furthermore, genes central
to the NFκB signalling pathway, downstream of TNF and IL signalling, are expressed
specifically after voluntary eccentric contractions in humans (Hyldahl et al., 2011;
Mahoney et al., 2008), supporting the existence of a pronounced inflammatory response
despite the likely absence of necrosis. Whilst myogenesis may not be required for
recovery following voluntary exercise, cell-culture work highlights that TNF-α impairs
the incorporation of [3H]-phenylalanine into protein in a dose-dependent manner (Frost,
Lang, & Gelato, 1997), whereas anti-TNF-α treatment in cachexic rats reduces protein
breakdown rates, measured by radioactive decay after [14C]-sodium bicarbonate injection,
by ~37% (Costelli et al., 1993). Thus, post-exercise inflammation likely influences
muscle protein turnover during recovery, although currently no data exist exploring this
interaction in humans.
Several studies have indicated that leukocyte accumulation may impair functional
recovery and, in rare instances, induce secondary damage to the muscle tissue (MacIntyre,
Reid, Lyster, Szasz, & McKenzie, 1996; Paulsen et al., 2010). By stratifying individuals
into “high responders” and “moderate responders” to eccentric-exercise-induced muscle
damage, Paulsen et al. (2010) identified a correlational relationship between leukocyte
accumulation over 24 h and isokinetic contractile function loss. Furthermore, in “high

26
responders” muscle function recovered to ~49% from ~68% under baseline values during
the first 6 h after exercise, but declined again to ~56% under baseline 24 h after exercise.
This secondary loss of force was not observed in “moderate responders”, who had lower
leukocyte counts and significantly attenuated loss in muscle function (~25%). In mice
deficient of CD18, a protein involved with neutrophil cellular adhesion and signalling,
Pizza, Peterson, Baas, and Koh (2005) observed attenuated isometric force loss following
eccentric contractions in contrast to wildtype mice. Furthermore, intramuscular
neutrophil content remained unchanged in CD18-hypomorphic mice after eccentric
contractions and was observed alongside significantly lower markers of oxidative
damage, as well as accelerated isometric force recovery over 7 days. Indeed, the
phagocytic activity and release of proteases and reactive oxygen species to break down
damaged tissue are believed to damage surrounding healthy tissue (Nguyen & Tidball,
2003). Together, these data would suggest that recovery speed may be inhibited by
aberrant inflammation.
Whilst leukocyte infiltration can impair recovery, reducing or blocking inflammatory
signalling altogether is equally detrimental (Chazaud, 2016; Peake et al., 2017). Single
nucleotide polymorphisms (SNPs) in chemokine ligand 2 (CCL2) and its receptor
chemokine receptor 2 (CCR2), which are required for macrophage chemotaxis and
muscle infiltration (Lu, Huang, Ransohoff, & Zhou, 2011), are associated with delayed
recovery over 10 days following voluntary eccentric exercise in humans (Hubal et al.,
2010). Furthermore, treatment with the pharmaceutical antioxidant N-acetylcysteine
(NAC) delays recovery from eccentric exercise, despite attenuating muscle leukocyte
infiltration, reducing markers of oxidative damage and suppressing signalling through the
NFκB pathway (Michailidis et al., 2013). This is likely explained by the phenomenon
whereby macrophages switch to an anti-inflammatory phenotype after the initial pro-
inflammatory
response
(Chazaud,
2016).
Anti-inflammatory
macrophages
release

27
cytokines such as transforming growth factor‐β1 and IL‐10 and directly support
myogenesis and myofiber growth in vitro (Arnold et al., 2007). The presence of anti-
inflammatory, Arginase 1-expressing macrophages has been verified in human muscles
following eccentric exercise with electrical stimulation, with these macrophages co-
localising with cells staining positive for myogenin (Saclier et al., 2013). Although it is
unclear whether anti-inflammatory macrophages directly support recovery in humans,
NAC treatment following voluntary eccentric exercise suppresses macrophage
appearance in muscle and reduces MyoD protein content (Michailidis et al., 2013). Thus,
it appears that a modicum of inflammation is required for recovery.
1.3.5
Muscle protein turnover following damage
From a whole-body perspective, protein turnover to facilitate healing and
gluconeogenesis increases dramatically following injury. Early studies in severely burned
patients showed that both whole-body protein synthesis and breakdown are greater versus
unburned controls, with this being ~100% greater as assessed by [15N]-glycine tracer
(Kien, Young, Rohrbaugh, & Burke, 1978), or ~40-50% with [13C]-leucine infusion
(Wolfe, Goodenough, Burke, & Wolfe, 1983; Wolfe, Goodenough, Wolfe, Royle, &
Nadel, 1982). However, in the muscle specifically, protein synthesis increases ~50%,
whereas muscle protein breakdown increases ~83%, creating more than two-fold greater
negative protein balance and net efflux of amino acids from the muscle tissue (160 ± 49,
versus 114 ± 66 nmol·min-1·100 mL leg volume-1 in unburned controls) (Biolo et al.,
2002). Moreover, α-actin and myosin heavy chain expression are suppressed by ~74%
and ~86%, respectively, in septic versus healthy rats (Hasselgren et al., 1991), meanwhile
ubiquitin and 20s proteasome mRNA increases three-to-four-fold (Tiao et al., 1997),
indicating a relative suppression of MPS and upregulation of breakdown. Nonetheless,

28
when damage occurs to the skeletal muscle itself, the process of MPS must equal or
surpass MPB such that damaged muscle proteins are replaced, without resulting in loss
of muscle mass or function from incomplete regeneration (Grogan, Hsu, & Skeletal
Trauma Research, 2011). Indeed, following unaccustomed resistance exercise in
untrained individuals, a model known to cause low-to-moderate muscle damage
(Clarkson, Nosaka, & Braun, 1992; Damas et al., 2016c), the rise in MPS is greater in
magnitude and duration than MPB (Biolo et al. (1995b); Phillips et al. (1997); discussed
above in more detail, see 1.2.1 Exercise). However, the effects of contraction per se are
difficult to separate, and very limited data exist exploring muscle protein turnover
following more damaging experimental models. Thus, the contribution of this process to
recovery is unclear.
One of the earliest studies to investigate protein turnover in response to muscle damage
was performed by Lowe et al. (1995). Hindlimb muscles of mice were forcibly lengthened
to induce muscle damage and then excised at 8 time-points over 14 days of recovery.
Rates of L-[U-14C]-phenylalanine incorporation into ex vivo muscle tissue were
suppressed by ~23% at 3 h after damage. From 3 h, a continuous increase in protein
synthesis was observed, surpassing baseline rates from 24 – 120 h after damage. Protein
breakdown, as measured by tyrosine release from muscle, was unchanged 0 – 6 h after
damage, but increased thereafter and plateaued at ~57% between 48 – 120 h. Whilst this
remains one of the most comprehensive studies of muscle protein turnover following
muscle damage to date, the authors observed ~55% loss in isometric torque production
and macrophage-infiltrated muscle fibres were observed in 6 out of 8 muscle cross-
sections. Therefore, these observations might reflect severe muscle damage and thus
applicability to exercise-induced muscle damage in humans may be limited. Supporting
this suggestion, caecal-ligation-puncture models of muscle damage and sepsis cause
inflammation-induced suppression of mTORC1 signalling and protein synthesis after 24

29
h, (Steiner, Crowell, Kimball, & Lang, 2015), later followed by an upregulation in MPS
after 10 days of recovery (Crowell & Lang, 2021). Conversely, this suppression is not
observed after 60 maximal voluntary eccentric contractions in humans, as myofibrillar
protein synthesis is ~62% greater over 1.5 – 4.5 h compared to rest (Moore et al., 2005).
Although muscle contraction alone increases rates of MPS independent of muscle
damage, myofibrillar protein synthesis is significantly greater over 8.5 h following
voluntary eccentric versus work-matched, concentric exercise (Moore et al., 2005). This
suggests an additional effect of eccentric exercise, which may reflect a demand for muscle
repair, in support of the rodent models previously discussed. However, rates of MPS
during recovery in humans are not well characterised. Traditional tracer incorporation
methods of measuring muscle protein synthesis in humans are limited to several hours in
order to reduce the chance of tracer recycling (Wolfe & Chinkes, 2005). Furthermore,
MPS cannot easily be reassessed at subsequent periods of recovery as tracer will continue
to be present in circulation after cessation of infusion. To circumvent this problem
Cuthbertson et al. (2006) used [13C]-leucine followed by [13C]-valine tracers to assess
myofibrillar protein synthesis between 0, 3 and 6 h, and again between 21 – 24 h after
bench stepping exercise. A delay in the rise of myofibrillar protein synthesis was
observed, being ~3.1-fold greater than baseline at both 6 and 24 h after exercise. However,
this rise was similar to a work-matched, concentrically exercised, contralateral leg, so the
stimulation of MyoPS was likely in response to muscle contraction, as opposed to the
demand for repair (Burd et al., 2010a; Miller et al., 2005; Wall et al., 2016).
An alternative method of assessing MPS over a prolonged period involves utilising
deuterium oxide (2H2O), which allows rates to be determined in “free-living” conditions
outside of a laboratory setting. Following consumption, deuterium rapidly (<20 min)
equilibrates
with
the
body
water
pool
and
alanine
is
subsequently
labelled
via
transamination (Dufner et al., 2005; MacDonald et al., 2013; Oshima & Tamiya, 1961).

30
If the body water pool remains appropriately enriched, application of 2H2O allows for the
characterisation of daily, cumulative protein synthesis rates, which would be appropriate
to capture the full recovery process. To date, two studies have employed this approach to
investigate rates of MyoPS during recovery from resistance exercise in recreationally
active (Waskiw-Ford et al., 2020) and resistance-trained males (Davies et al., 2020). Over
a 96 h period following resistance exercise Waskiw-Ford et al. (2020) reported ~21% loss
in peak torque after 48 h and ~72% greater rates of myofibrillar protein synthesis
compared to rates measured pre-exercise using the single biopsy technique. Conversely,
Davies et al. (2020) failed to observe a change in rates of MyoPS over 5 days, despite
peak torque decreasing ~20% in response to exercise. However, counter-movement jump
height was largely unaffected by resistance exercise and individuals were accustomed to
resistance exercise (~2.5 y experience), so it is unclear whether muscle damage was
induced in this instance.
Together, although these findings tend to suggest that recovery from exercise-induced
muscle damage aligns with elevated rates of mixed muscle and myofibrillar protein
synthesis, the relative importance of this process to recovery remains unknown.
1.4
Nutritional strategies to support recovery from muscle damage
1.4.1
Protein and amino acids
Given that rates of MPS are greater with eccentric exercise (Moore et al., 2005), amino
acid availability may be a limiting factor determining recovery. As such, many studies
have focused on augmenting protein intake to support recovery from muscle damage,
with mixed outcomes. An overview of these studies that employ a single bout of
resistance-based exercise with ingestion of protein and other amino acid sources is shown
in Table 1.1. Branched-chain amino acid (BCAA) consumption pre-exercise has been

31
shown to attenuate muscle soreness and the decline in MVC strength following 140 squat
repetitions (Shimomura et al., 2010). In a similarly untrained group consuming 3.6 g of
amino acids (AA) pre- and post-maximal eccentric bicep contractions, continued
supplementation over 5 days suppressed the rise in soreness, CK, and arm circumference,
although did not aid the recovery of MVC (Nosaka, Sacco, & Mawatari, 2006).
Interestingly, these differences were not observed when AAs were provided only on the
day of exercise, suggesting that sustaining exogenous amino acid availability is necessary
to aid recovery (Nosaka et al., 2006). In support of this, BCAA supplementation (10 g,
consumed twice daily) for 8 days prior and 4 days following drop jump exercise
attenuated the rise in plasma CK and muscle soreness and showed greater recovery of
MVC strength (Howatson et al., 2012). In addition to isolated amino acid supplements,
protein blends such as whey or casein have been administered due to their complete amino
acid profile (Witard, Wardle, Macnaughton, Hodgson, & Tipton, 2016) and potent
stimulatory effect on MPS (Tang, Moore, Kujbida, Tarnopolsky, & Phillips, 2009).
Accordingly, 31 g whey protein hydrolysate ameliorated the fall in MVC and peak
isokinetic torque of the knee extensors over 24 h following 100 maximal eccentric
contractions in untrained individuals (Ives et al., 2017).
Although data largely appear to support the use of protein or amino acid supplementation
(Davies et al., 2018), the lack of direct evidence from muscle biopsy samples (as
demonstrated in Table 1.1) means that it is difficult to conclude how given supplements
are effective. Nonetheless, Farup et al. (2014a) investigated the presence of satellite cells
in muscle biopsy samples collected after eccentric exercise. Satellite cells exert myogenic
properties (Brack & Rando, 2012) and proliferate in muscle following eccentric exercise
(Mikkelsen et al., 2009). Furthermore, satellite cells have a key role in recovery from
severe muscle damage (Relaix & Zammit, 2012). Indeed, participants fed a combined
protein and carbohydrate beverage (1:1 ratio, 56 g in total) demonstrated a greater number

32
of satellite cells per muscle fibre compared to participants fed an isocaloric placebo 48 h
post damaging exercise (Farup et al., 2014a). However, no group differences in functional
outcomes such as soreness, MVC strength or serum CK were observed, so their role in
recovery is unclear. Furthermore, as previously discussed, the role of satellite cells
following voluntary eccentric exercise is debated due to the likely absence of severe
muscle damage (Grounds, 2014). Subsequent investigation on the biopsy samples
collected in this study revealed that although eccentric exercise increased phosphorylation
of mTORSer2448 and p70S6KThr389 at 3 h post-exercise, no group differences were observed
at this time point or at 24 or 48 h (Rahbek, Farup, de Paoli, & Vissing, 2015).
Additionally, FOXO1Ser256 and FOXO3aSer253 phosphorylation was suppressed at all
timepoints post-exercise, which may suggest a possible increase in ubiquitin-proteasome
activity and/or insulin resistance due to muscle damage (Kirwan et al., 1992). However,
these were unaffected by intervention and similar changes were observed in the control
leg. Furthermore, no changes in MuRF1 protein content were observed over time or
between groups (Rahbek et al., 2015), and so it is unlikely this response reflects recovery
from muscle damage per se.
More direct evidence employing stable isotope approaches is seemingly limited to three
studies (Davies et al., 2020; Hamarsland et al., 2017; Waskiw-Ford et al., 2020). In a
group of resistance-trained individuals, rates of MPS were measured immediately after a
bout of resistance exercise followed by the provision of one of three different milk protein
derivatives, with MVC measured concurrently and over the following 24 h period
(Hamarsland et al., 2017). Consumption of a whey protein product or a proprietary milk
protein product increased rates of MPS versus milk alone, with the latter of the two
products demonstrating greater phosphorylation of p70S6KThr389 and suppression of 4E-
BP1Thr37/46. Furthermore, recovery of MVC was delayed only on the milk group,
suggesting stimulation of MPS contributes to recovery. Nonetheless, methodological

33
issues confound the study results, as the exercise stimulus was moderate given that the
participants were resistance-trained (4 sets of 8 repetitions of leg press and knee extensor)
and the two groups exhibiting an improved recovery profile completed the study in a
cross-over fashion, whereas individuals in the milk comparator group were exposed to
muscle damage once. Due to the repeated bout effect, it is unsurprising that the milk group
exhibited delayed recovery as participants in this group were only exposed to damage
once. In a subsequent study, recreationally active individuals were provided 12 g leucine-
enriched essential amino acids (LEAA) per day following resistance exercise (Waskiw-
Ford et al., 2020). Whilst LEAAs did not support the recovery of peak isokinetic torque
measured at various speeds, the sum of all torques produced over isokinetic and isometric
strength and function tests were ~10% greater over 96 h versus isocaloric placebo.
However, rates of MyoPS over this time were unaffected by LEAAs (Waskiw-Ford et al.,
2020), suggesting that recovery is not underpinned by MyoPS. Nonetheless, muscle
damage was induced bilaterally, whereas function and muscle protein synthesis rates were
determined contralaterally. Testing of muscle function may provide a contraction
stimulus, which when combined with exogenous amino acids likely promotes rates of
MPS over and above the effects of amino acids alone (Biolo et al., 1997). Thus, measured
rates of MyoPS may not reflect true rates of MyoPS in the leg in which function was
measured. In trained individuals, whey protein ingestion over a period of intensified
resistance exercise was demonstrated to not stimulate rates of MyoPS, or influence
indices of recovery (Davies et al., 2020). However, if MyoPS is purported to explain the
recovery of muscle function, it is unsurprising that recovery did not differ given the
comparable rates of MyoPS that were measured. Furthermore, as previously discussed, it
is questionable whether the exercise induced muscle damage. Clearly, differences
between, and flaws within, study designs preclude any firm conclusions being made about
the mechanisms that underpin recovery. Given the heterogeneity in outcomes with protein

34
supplementation, careful consideration needs to be given to study design (detailed in
Table 1.1) in order to observe a beneficial effect of protein, which is a prerequisite to
exploring mechanisms that may underpin recovery.
1.4.2
Polyphenols
Plants produce many phenolic and polyphenolic compounds through the metabolism of
phenylalanine in the phenylpropanoid pathway (Duthie, Gardner, & Kyle, 2003). These
compounds are involved in a diverse range of functions, including growth, stability,
disease resistance and pigmentation. Phenolic compounds are characterised by two or
more hydroxyl groups attached to one (or more, in the case of polyphenols) benzene rings
and based on their specific structural arrangement are categorised into four main groups:
flavonoids, lignans, phenolic acids and stilbenes. Flavonoids in particular are referred to
as chain-breaking antioxidants because these hydroxyl groups readily donate H+ ions to
free radicals. The resultant aroxyl radicals are stable enough to avoid chain-propagating
reactions, as benzene rings support unpaired electrons in their delocalised π-electron
system (Bors, Michel, & Stettmaier, 2001; Duthie et al., 2003).
In addition to the various classes of naturally occurring phenolic compounds in fruit,
many polyphenols may be bound to other functional groups affecting their chemical,
physical and biological properties. For example, many classes of flavonoids are
glycosylated, which after ingestion may become deglycosylated and in turn more
lipophilic (Brown, Khodr, Hider, & Rice-Evans, 1998). Glucuronidation, sulfation and
methylation reactions occur in the small intestine, colon and liver, producing various
metabolites in that are then present in circulation (Scalbert & Williamson, 2000).
Illustrating the varied metabolism, healthy male participants consumed 500 mg of [13C5]-

35
cyanidin-3-glycoside, which peaked in serum after 2 h. At 6 h, concentrations returned to
baseline whereas 17 metabolites were detectable, lasting up to 48 h post-ingestion.
Although data are scarce on the potency of the numerous forms of phenolic compounds,
both those which are naturally occurring and those that are metabolised following
consumption, the general use of polyphenols has gained considerable attention in
promoting both health and exercise performance (Bowtell & Kelly, 2019; Garcia-Conesa
& Larrosa, 2020). A growing body of evidence supports the use of fruit-derived
polyphenols to accelerate recovery from muscle damage specifically (Ammar et al., 2018;
Bowtell & Kelly, 2019). An overview of these studies investigating recovery from
exercise involving an eccentric component is given in Table 1.2. Pomegranate in
particular, which is rich in flavonoids (Gomez-Caravaca et al., 2013), has been shown to
improve recovery of elbow flexor and knee extensor muscles when consumed after
voluntary eccentric exercise (Machin et al., 2014; Trombold, Barnes, Critchley, & Coyle,
2010; Trombold, Reinfeld, Casler, & Coyle, 2011). In resistance-trained men, 60
eccentric contractions of the elbow flexors reduced isometric MVC to ~70% baseline
strength when measured after 2 h. In a cohort consuming pomegranate juice daily
(providing ~1240 mg·d-1 polyphenols), MVC averaged ~94% of baseline between 2 –
168 h of recovery, significantly greater than the placebo group at ~89% of baseline
(Trombold et al., 2011). However, in the same cohort, pomegranate did not support MVC
recovery in the knee extensors. Nonetheless, only a moderate loss of force was observed
in this muscle group (~19%, versus ~30% in elbow flexors), suggesting that pomegranate
supports recovery when muscle damage is greater (Trombold et al., 2011). In untrained
individuals, Machin et al. (2014) observed greater MVC recovery in both knee extensors
and elbow flexors with daily supplementation of pomegranate juice over 4 days following
eccentric exercise. Supplementation provided either 650 mg or 1300 mg polyphenols,
which were observed to be equally as effective versus placebo (Machin et al., 2014). As

36
is the case with studies employing protein to support recovery, direct evidence for a
mechanism to explain the accelerated recovery with pomegranate is largely absent
(exemplified in Table 1.2). Data published elsewhere show that consumption of 500 mL
pomegranate juice per day increases the concentration of enzymatic (i.e., catalase and
glutathione peroxidase) and non-enzymatic (i.e., uric acid and total bilirubin) antioxidant
biomarkers following resistance exercise in trained individuals (Ammar et al., 2017). In
the same cohort, pomegranate juice increased maximum strength and total volume lifted
in a training session performed 48 h later by ~8% (Ammar et al., 2016). Similarly,
pomegranate supplementation lowers protein carbonylation following aerobic exercise
(Fuster-Munoz et al., 2016), which has been associated with accelerated recovery from
maximal voluntary eccentric exercise (Draganidis et al., 2017). As previously discussed,
full inhibition of inflammation appears detrimental to recovery in humans, so the apparent
anti-inflammatory effects of pomegranate are difficult to reconcile. However, in rats, 20
mg·kg-1·d-1 of grapeseed derived proanthocyanidins reportedly suppressed skeletal
muscle neutrophil content following contusion injury (Myburgh, Kruger, & Smith, 2012).
Whilst there were no differences compared to placebo in the magnitude of cells staining
for F4/80 and fibres staining for embryonic myosin heavy chain and/or fibres with
centrally located nuclei, indicative of macrophage content and myofiber regeneration,
respectively, the peaks occurred ~2 and ~4 days earlier with proanthocyanidin treatment
(Myburgh et al., 2012). Thus, pomegranate may support recovery through modulating,
rather than fully suppressing post-exercise inflammation, serving to inhibit neutrophil
activity whilst permitting macrophage accumulation. Therefore, combining protein with
polyphenol may be an effective strategy to accelerate recovery, and subsequently to
enable an investigation into the underpinning mechanisms.

37
1.5
Aims
Taken together, the overarching hypothesis is that protein and polyphenol
supplementation will accelerate recovery from muscle-damaging eccentric exercise and
resistance-type exercise training, and that by using such models, an increase in MyoPS
and a dampening of inflammation will be identified as essential for recovery and
adaptation.
Thus, the present thesis aims to address the following objectives:
1)
Whether a combined protein-polyphenol nutritional intervention (PPB) results in
post-prandial aminoacidaemia and increases rates of the whole body and
myofibrillar protein synthesis.
2)
Whether increased rates of myofibrillar protein synthesis, associated signalling
pathways, and reduced transcription of muscle protein breakdown and
inflammatory pathways explain accelerated recovery from muscle-damaging
eccentric exercise with PPB.
3)
Whether increasing rates of myofibrillar protein synthesis further supports the
gains in strength and hypertrophy during a period of resistance exercise training
with PPB.

38
Table 1.1. Studies investigating recovery from muscle-damaging exercise with ingestion of protein or other amino acid sources
Study
Subjects
Design
Damaging
protocol
Supplement
Control
Measurement
Duration
Muscle function
Skeletal muscle
metabolism
Nosaka
(2006)
et al.
14 males
Untrained
Crossover
900 bicep
contractions at
3.6 g AA
30min pre
and
Non-isocaloric
placebo
96 h
MVC ↔
n/a
Experiment 1
Nosaka et al.
(2006)
Experiment 2
24 males
Untrained
9% 1-RM
Crossover 900 bicep
contractions at
9% 1-RM
immediately post EX
3.6 g AA
30min pre and
immediately post EX
2x daily for 3 days
No dietary
control
Non-isocaloric
placebo
No dietary
control
96 h MVC ↔ n/a
Cockburn, 24 males Parallel 60 eccentric Chocolate milk
(33
g Water 48 h Peak isokinetic n/a
Hayes, French,
Stevenson, and
St Clair Gibson
(2008)
Team sport
players
knee extensor
contractions
PRO + 118 g CHO)
Milk (34 g PRO + 49 g
CHO)
CHO (64 g)
No
control
dietary
torque ↑
Total work ↑
Buckley
et
al.
43 males
Parallel
100
eccentric
Immediately and 2 h
post EX
25 g WP isolate
Flavoured
24 h
MVC
(↑
for WP
n/a
(2010)
Untrained
knee extensor
contractions
25 g WP hydrolysate
Immediately, 2h and
22h post EX
water
No dietary
control
hydrolysate;
↔ for WP isolate)
Cooke,
17 males
Parallel
40 repetitions
1.5 g·kgBM-1
WP
Iso-caloric
14 d
MVC ↑
n/a
(2010)
leg curls at
120% 1-RM
Jackman,
Witard,
Jeukendrup, and
Tipton (2010)
24 males
Non-
resistance
trained
Parallel
120 eccentric
knee extensor
contractions at
120% 1-RM
7.3 g BCAA
4x daily
Non-isocaloric
placebo
Full dietary
control
72 h
MVC ↔
n/a
Shimomura et
al. (2010)
12 females
Untrained
Crossover
140 unloaded
squats
5.5 g BCAA
Pre-EX
Iso-caloric
CHO
72 h
MVC ↑
n/a
Rybalka,
Untrained
each of
leg
hydrolysate
CHO
Peak
isokinetic
Stathis,
Cribb,
press,
leg
Daily for 14 days
No
dietary
torque ↔
and
Hayes
extension
and
control

39
No dietary
control
Howatson et al.
12 males
Parallel
100
drop-
10 g BCAA
Non-isocaloric
96 h
MVC ↑
n/a
(2012)
Team sport
jumps
2x
daily
for
12
days
placebo
Vertical
jump
players
(including 7-day
No dietary
height ↔
loading phase)
control
Farup et al.
(2014a)
24 males
Recreational
ly active
Parallel 150 maximal
eccentric knee
extensor
contractions
Additional 20 g pre- and
post-EX
28 g WP hydrolysate +
CHO
3x per day for 3 days
Iso-caloric
CHO
No dietary
control
168 h MVC ↔ SC content ↑
mTOR signalling
pathway ↔1
↓FOXO transcription
factors1
Draganidis et al.
(2017) 11 males
Resistance
trained
Crossover 300 maximal
eccentric knee
extensor
contractions
WP + casein blend (20 g
PRO)
Immediately, 3 h, 6 h
and 9 h post EX
1x per day thereafter for
8 days
Iso-caloric
placebo
Individualised
meal plans
provided
192 h Peak
isokinetic/isometric
torque ↑
Proteasome activity ↔
NFκB phosphorylation
↓
HSP70 ↓
Hamarsland et
al. (2017) 22 males and
females
Resistance
trained
Parallel /
crossover 32 repetitions
each of leg
press and knee
extension at
100% 8RM
WP concentrate (20 g
PRO)
Native WP (21 g PRO)
Immediately and 2 h
post EX
Iso-caloric
milk
Full dietary
control
24 h MVC ↑ 5 h FSR ↑
Ives et al.
(2017) 60 males
Untrained Parallel 100 maximal
eccentric knee
extensor
contractions
31 g WP hydrolysate
31 g WP hydrolysate +
100 mg berry powder
Immediately post, 6h
post and 22h post EX
Iso-caloric
CHO
Generic meal
plans provided
24 h MVC ↔
Peak isokinetic
torque ↑
n/a
Kim, Lee, and
Lee (2017) 32 males
Untrained Parallel 50 maximal
eccentric
elbow flexor
contractions
1.5g·kgBM-1 WP
Either pre, immediately
post, or pre- and post-
EX
Non-placebo
control
No dietary
control
96 h MVC ↔ n/a

40
Waskiw-Ford et
20 males
Parallel
45-60
4 g leucine enriched
Isocaloric
96 h
MVC ↔
96 h FSR ↔
al. (2020)
Recreational
repetitions
of
AAs
placebo
Slow
peak
ly active
leg press and
3x per day for 4 days
Full dietary
isokinetic
torque
Davies et al.
(2020)
16 males
Resistance
trained
leg extension
Parallel Sets
of
back
squats until
failure
0.33 g·kgBM-1 WP
For 7 days post EX
control at 1.2
g·kgBM-1·d-1
Isonitrogenous
nonessential
amino acid
Full dietary
control at 1.7
g·kgBM-1·d-1
↔
Fast peak isokinetic
torque ↔
Total torque ↑
168 h Squat MVC ↔
Countermovement
jump height ↔
144 h FSR ↔
RM: repetition maximum; AA: amino acid; EX: exercise; MVC: maximum voluntary isometric contraction; PRO: protein; CHO: carbohydrate;
WP: whey protein; BCAA: branched-chain amino acids; SC: satellite cell; FSR: fractional synthetic rate; ↑: positive effect of intervention; ↔: no
effect of intervention; ↓: negative effect of the intervention. 1Data presented in Rahbek et al. (2015).

41
Table 1.2. Studies investigating recovery from muscle-damaging exercise with ingestion of fruit-derived polyphenols.
Study
Subjects
Design
Damaging
protocol
Supplement
Control
Measurement
Duration
Muscle
function
Skeletal
muscle
metabolism
Connolly,
14 males
Crossover
(using
40 maximal
Tart cherry juice
Isotonic
sugar
96 h
MVC ↑
n/a
McHugh,
Non-resistance
contralateral
eccentric elbow
(600 mg phenolic
placebo
Padilla-Zakour,
Carlson, and
trained
limbs)
flexor
contractions
compounds; 40
mg total
No
control
dietary
Sayers (2006)
Bowtell,
10 males
Crossover
100 knee
anthocyanins)
twice daily
4 days pre and 2
days post ex
Montmorency
Iso-caloric
48 h
1-RM ↑
n/a
Sumners, Dyer,
Fox, and Mileva
(2011)
Trombold et al.
(2010)
Trombold et al.
Resistance
trained
16 males
Recreationally
active
17 males
Crossover
Crossover
(using
extensions at 80%
1-RM
40 maximal
eccentric elbow
flexor
contractions
60 maximal
cherry juice (547
mg total
anthocyanins)
7 days pre and 2
days post EX
Pomegranate juice
(650 mg phenolic
compounds) twice
daily
5-day pre and 4
days post EX
Pomegranate juice
placebo
No dietary
control
Iso-caloric
placebo
No dietary
control
Iso-caloric
96 h
168 h
MVC ↑
Elbow
n/a
flexor n/a
(2011)
Resistance
contralateral
eccentric elbow
(495 mg tannins;
placebo
MVC ↑
trained
limbs)
flexor
contractions
60 eccentric knee
extensor
contractions at
110% 1-RM
96 mg
anthocyanins; 30
mg ellagic acid)
twice daily
8 days pre and 7
days post EX
No dietary
control
Knee
MVC ↔
extensor
McLeay
et
al.
10 females
Crossover (using
300
maximal
Blueberry
Isocaloric
60 h
MVC ↑
n/a
(2012)
Recreationally
contralateral
eccentric
smoothie (168 mg
placebo
Isokinetic
active
limbs)
contractions
phenolic
compounds;
97
Dietary
control on day
of EX
(eccentric
concentric)
torque ↔
and
peak

42
mg anthocyanins;
per 100 mL)
3 beverages on
day of EX, once-
daily thereafter
Average
isometric and
isokinetic
(eccentric and
concentric)
torque ↔
Machin
et
al.
45 males
Parallel
20
min
downhill
Pomegranate juice
Iso-caloric
96 h
Knee
extensor
n/a
(2014)
Recreationally
running
at
-10%
(650 mg phenolic
placebo
MVC ↑
active gradient
40 repetitions of
isotonic eccentric
elbow flexor
contractions at
100% 1-RM
compounds) once
daily
Pomegranate juice
(650 mg phenolic
compounds) twice
daily
4 days pre and 4
days post EX
No dietary
control Elbow flexor
MVC ↑
Levers et al.
(2015) 23 males
Resistance
trained
Parallel 100 repetitions of
back squat at 70%
1-RM
Tart cherry
powder (600 mg
phenolic
compounds; 40
mg anthocyanins)
8 days prior and 2
days post EX
Rice flour
placebo
No dietary
control
48 h Total isokinetic
work ↔ n/a
Ammar et al.
(2016) 9 males
Resistance
trained
Single-arm
(placebo then
active condition)
6 repetitions of
snatch, clean and
jerk, and back
squat at 85% 1-
RM
6 repetitions of
snatch, clean and
jerk, and back
squat at 90% 1-
RM
Pomegranate juice
(2560 mg
phenolic
compounds)
Immediately pre
EX, three times
daily post EX
Non-caloric
placebo
No dietary
control
48 h Total volume
lifted ↑
Maximum load
lifted ↑
n/a

43
Beals et al.
(2017) 29 males and
females
Recreationally
active
Parallel Multiple sets of
knee extensor
eccentric
contractions, until
50% loss of peak
torque
Tart and black
cherry extract
(733 mg phenolic
compounds)
5 days pre and 7
days post EX
Iso-caloric,
protein and
carbohydrate
matched
placebo
No dietary
control
168 h Peak isokinetic
torque ↔ n/a
Lamb
et
al.
36
non-
Parallel
50
maximal
Pomegranate juice
Iso-caloric 96 h MVC ↔ n/a
(2019)
resistance
eccentric
elbow
(879 mg phenolic
placebo
trained
flexions
compounds; 49
No dietary
mg anthocyanins)
control
Tart cherry juice
(295 mg phenolic
compounds; 8 mg
anthocyanins)
Twice per day for
5 days pre and 4
days post EX
RM: repetition maximum; EX: exercise; MVC: maximum voluntary isometric contraction torque or force; ↑: positive effect of intervention; ↔:
no effect of intervention; ↓ =: negative effect of the intervention.

44
Chapter 2 - General Methods

45
2.1
Study data collection
The following chapter details the methods used in Chapters 3, 4 and 5.
2.1.1
Ethical approval
The University of Exeter’s Sport and Health Sciences Research Ethics Committee approved all
experimental protocols described in Chapter 3 (Proposal Ref No: 180509/B/03), Chapter 4
(Proposal Ref No: 161026/B/06) and Chapter 5 (Proposal Ref No: 171206/B/09). All protocols
were conducted in accordance with principles detailed in the Declaration of Helsinki (World
Medical, 2013).
2.1.2
Participant recruitment and screening
Participants were recruited through opportunity/convenience sampling of the student and staff
population of the University of Exeter, as well as from the local community. Physical posters
were affixed to noticeboards and electronic versions were posted on social media. The
researchers’ university email addresses were available on the posters for prospective
participants to contact should they require more information or express interest in taking part.
After expressing interest, prospective participants were sent an information sheet detailing, in
lay language, the purpose of the study and the experimental procedures, as well as the risks and
benefits to taking part. Subsequently, they were invited to attend a screening visit >24 h later
at the Sports and Health Sciences department on St Luke’s Campus, University of Exeter.
During this visit, the participant information sheet was discussed in detail, including the study
timeframe, protocol, procedures and the participant’s right to withdraw at any time. Participants
then provided written informed consent and completed a general health questionnaire to assess

46
suitability based on the inclusion and exclusion criteria identified a priori. Participants’ body
weight (Seca digital column scale SEC-170, Seca, Hamburg, Germany) and height (Seca
stadiometer SEC-225, Seca) was recorded in the laboratory. All participants were instructed on
how to complete a habitual diet diary and were asked to record 2 weekdays and 1 weekend day.
Specifically, participants were asked to record time of consumption, the food or drink, the
brand, quantity used, and whether any was left over that was not accounted for in the original
weight (food diary template presented in Appendix 3.3). Participants were provided digital
scales (Salter 1036 Electronic Kitchen Scales, Salter Housewares, Kent, UK) and were asked
to weigh each ingredient in its raw/uncooked form where possible.
Following enrolment to the study, all participants were randomly allocated to a treatment label
and assigned a participant identification number to protect their identity during data collection.
2.1.3
Familiarisation to testing procedures
In Chapters 4 and 5, participants visited the laboratory at least 48 h prior to the start of the study
for familiarisation with the visual analogue scale (see 2.1.4 Muscle Soreness) and isokinetic
dynamometer (Biodex System 3, Biodex Medical Systems Inc., NY).
Participants were secured in the isokinetic dynamometer with restraining straps crossing the
torso, waist and exercised leg to prevent extraneous movement during muscle contraction. Hip
joint angle was set at 85 degrees and the lateral condyle of the femur was aligned with the axis
of rotation of the dynamometer. An ankle strap contacted the leg above the malleolus medialis,
and the dynamometer arm was aligned parallel to the tibia. Participants extended and flexed
their knee through its full range of movement to ensure the restraining straps or seat did not
impede knee extension and flexion and that the hip, knee and ankle were aligned to ensure
47
No pain
Worst possible
pain
movement entirely in the sagittal plane. The seat and dynamometer positions were measured,
recorded, and repeated for all subsequent visits.
For Chapter 4, participants were familiarised with one set of 30 maximal, isokinetic, concentric,
knee extensor contractions (see 2.1.5 Muscle Function), followed by 5 sub-maximal eccentric
contractions. A full set of 30 maximal eccentric contractions was deliberately not used to
reduce the risk of inducing any muscle damage prior to the start of the data collection. For
Chapter 5, participants were also familiarised with isometric voluntary contractions, performed
at 50%, 75% and 2 x 100% of maximum effort and separated by 30 s rest, as well as 3 x
maximal, isokinetic, concentric, knee extensor contractions to familiarise with the
measurement of peak isokinetic torque. Finally, this was repeated with the participant’s
contralateral leg.
2.1.4
Muscle soreness
Muscle soreness was measured by a 100 mm visual analogue scale (VAS; Figure 2.1).
Participants were asked to sit with their feet shoulder-width apart and knees bent at 90 degrees
flexion. Then, participants were given the standardised instruction to: “stand up, using both
legs equally, and indicate the sensation of pain”, by drawing vertical line intersecting the VAS
between ‘No pain’ and ‘Worst possible pain’.
Figure 2.1. Visual Analogue Scale (VAS) used to assess muscle soreness upon standing from
a chair.
48
The use of a 100 mm VAS has been previously validated as a reliable measure of pain, with
paired measurements intraclass correlation coefficient of 0.97, indicating excellent reliability
(Bijur, Silver, & Gallagher, 2001).
2.1.5
Muscle function
Following a brief warm-up set of 5 submaximal isokinetic concentric contractions, participants
performed 30 maximal isokinetic knee extensor contractions using the isokinetic
dynamometer. Angular velocity was 75 degrees·s-1 and knee joint range of motion was set at
80 degrees equidistant to full flexion and full extension, in order to capture a region of peak
torque production (Marginson & Eston, 2001; Walker & Schrodt, 1974).
Figure 2.2. Torque-time curve of 30 maximal isokinetic knee extensor contractions
performed at 75 degrees· s-1 between a range of motion equidistant to full-flexion and full
extension using the isokinetic dynamometer. A custom-made script was used to calculate the
area underneath the curve of each repetition.
Force data were sampled at 2000 Hz using an analogue-to-digital converter (Power1401-3A,
Cambridge Electronic Design Ltd., Cambridge, UK) connected to a computer running Spike2
software (Cambridge Electronic Design Ltd) to produce a torque-time curve (Figure 2.2) using
0.01 s averages for off-line analysis.
49
A custom-made script identified the beginning and end of each repetition automatically, from
which area under the curve was calculated (J). Data were then expressed relative to the
contralateral, control leg (i.e., non-damaged or untrained leg; %CON or %U).
Figure 2.3. Torque-time curve of a 3 s maximal isometric knee extensor contraction performed
at 75 degrees flexion (full extension = 0 degrees). This was repeated 3 times and the peak
torque value was determined using a custom-made script.
2.1.6
Muscle strength
Muscle strength was determined as maximal voluntary isometric contraction torque. This was
performed at 75 degrees from full knee extension (0 degrees), as this has previously been
reported to be the angle of peak torque production in males and females (Hicks et al., 2016;
Marginson & Eston, 2001). After a task-specific warm-up consisting of 3 s isometric
contractions at 50% (x2), 75% (x1), and 90% (x1) of perceived maximal effort, participants
performed 3 x 3 s maximal voluntary contractions, separated by 60 s. Participants were
instructed to kick as hard as possible and received verbal encouragement throughout each
contraction. Data were recorded as described above (see 2.1.5 Muscle Function; Figure 2.3). A
custom-made script was used to identify the peak isometric torque during each attempt. The

50
maximum value attained over the 3 repetitions was determined as the maximal voluntary
isometric contraction torque and expressed relative to the untrained control leg (%U).
2.1.7
Dietary control
Full dietary control was employed for the duration of the study protocols described in Chapter
4 (14 days) and the duration of the acute measurement period described in Chapter 5 (2 days).
A list of meals and snacks was created based on their simplicity and ease of preparation. Prior
to enrolment, participants were given the opportunity to indicate whether they disliked any
foods that appeared on the list (Appendix 3.2). For the study detailed in Chapter 4, a different
meal plan was created for each day of the week, such that plans were repeated once over the
14-day protocol. In Chapter 5, a meal plan was created for each of the 2 days of the acute
measurement period pre-training.
Daily energy requirements were calculated based on the Henry equation (Henry, 2005)
multiplied by an activity factor of 1.6 in order to keep participants in energy balance. Body
mass was recorded on each laboratory visit so that the daily energy intake could be adjusted if
required. The controlled diet was clamped at 1.2 g·kg body mass-1·d-1 of dietary protein, which
is within American College of Sports Medicine guidelines to support metabolic adaptation
(Thomas, Erdman, & Burke, 2016) but importantly, below current guidelines to maximise
muscle protein anabolism (Morton et al., 2018). The target macronutrient composition was
50% to 55% of total daily energy intake (en%) from carbohydrates, 30% to 35% of en% from
fat, 10% to 15% of en% from protein, and 2% of en% from dietary fibre. Breakfast, lunch,
dinner and snacks were individually weighed and packaged in a larger container corresponding
to each day of the week (Figure 2.4). Participants were provided with a form (Appendix 3.2) to
record whether a portion of food was consumed and the time of consumption. Step-by-step

51
instructions on how to cook the evening meal were included to increase compliance.
Participants returned the forms and any uneaten food, allowing for compliance to be quantified.
Of all energy provided in the controlled diets, 97.2 ± 0.8% was consumed.
Figure 2.4. Boxes containing breakfast, lunch, dinner and snacks. Ingredients were
individually weighed to provide energy balance and clamp daily protein intake at 1.2 g·kg body
mass-1. Each box contains all food for 1 day, where size permitted. Each box contained a recipe
card and a form to record whether each ingredient was consumed
2.1.8
Muscle biopsy
Muscle biopsies were collected from the mid-region of the m. vastus lateralis, by using the
percutaneous muscle biopsy technique modified for suction (Tarnopolsky, Pearce, Smith, &
Lach, 2011). The area was shaved clean and sterilised with an antiseptic solution.
Approximately 2 mL of 2% lidocaine solution was injected subcutaneously before an ~0.8cm
incision was made at the skin and muscle fascia below. The Bergström biopsy instrument was
guided through the incisions into the muscle and moderate suction was applied. Afterwards,
the sample was removed from the instrument, rapidly blotted of blood and dissected of

52
connective tissue, and frozen in liquid nitrogen cooled-isopentane. The target yield was 50-100
mg. Once frozen, samples were aliquoted and stored at -80°C for further analysis.
Data exist showing that the biopsy procedure per se can induce ultrastructural (Staron et al.,
1992) and metabolic (Malm et al., 2000; Vissing, Andersen, & Schjerling, 2005) perturbations
to the muscle tissue, particularly if incisions are made in close proximity or from the same
sampling site (Aronson et al., 1998). Nonetheless, this finding is not universal (Lundby et al.,
2005) and incision sites placed >2.5 cm apart appear not to influence the transcriptomic or
protein response (Frydelund-Larsen et al., 2007; Murton et al., 2014). Thus, in the present
studies, the first biopsy in each leg was taken in the distal part of the muscle and each
subsequent biopsy was taken approximately 2.5 cm proximal to the previous one. Where
contralateral study designs were employed (i.e., Chapters 4 and 5), a biopsy was taken from
the control leg at each time point as an extra level of control.
2.1.9
Plasma amino acid extraction
Plasma samples were defrosted at room temperature and deproteinised using an equal volume
of 15% sulphosalicylic acid (weight/vol %). Following centrifugation at 4000 x g for 10 min
at 4°C, the supernatant was passed over cation exchange resin columns (100 – 200 mesh; H+
form; Dowex 50WX8; Sigma-Aldrich Company Ltd., Dorset, UK). Columns were rinsed with
1 mL ddH2O, 6 mL 0.5 M acetic acid, 5 mL ddH2O and eluted with 2 mL 6 M ammonium
hydroxide (NH4OH), before being dried under vacuum and stored at -20°C for further analysis.
The concentration of all samples was measured relative to a curve of amino acid standards at
15.60, 31.25, 62.50, 120.00, 250.00 and 500.00 μM. An internal standard (10 μL of 2 mM
norleucine) was added to an additional set of 28 samples (8 x fasted samples, 10 x PPB fed
samples, 10 x PLA fed samples) prior to deproteinisation. These were run alongside a separate

53
standard curve containing 5 μL of 2 mM norleucine and divided by the concentration
determined when measured without the internal standard to obtain a correction factor for
extraction efficiency. The extraction efficiencies are displayed in Table 2.1. A further 20
samples were pooled to calculate inter-sample coefficient of variation (CV), calculated as;
leucine: 10.5%; isoleucine: 6.6%; valine: 11.1%; phenylalanine: 5.1%; tyrosine: 4.2%.
Table 2.1 Amino acid extraction efficiency
Fasted
PLA
PPB
(n = 8)
(n = 10)
(n = 10)
Leucine (% yield)
13.9 ± 0.6
14.6 ± 0.6
12.4 ± 0.5
Isoleucine (% yield)
20.7 ± 0.6
24.9 ± 1.2
16.6 ± 0.8
Valine (% yield)
12.0 ± 0.5
12.3 ± 0.4
11.3 ± 0.4
Phenylalanine (% yield)
25.4 ± 0.6
26.9 ± 1.3
24.3 ± 0.4
Tyrosine (% yield)
30.4 ± 1.5
30.7 ± 1.7
30.2 ± 0.6
Values represent mean ± SEM
2.1.10
Muscle amino acid extraction
Myofibrillar protein fractions were isolated from ~50 mg wet weight muscle tissue. Tissue was
homogenised in 7.5 μL·mg-1 ice-cold homogenisation buffer (50 mM Tris·HCl pH 7.4, 1 mM
EDTA, 1 mM EGTA, 10 mM β-glycerophosphate salt, 50 mM NaF and 0.5 mM activated
Na3VO4; Sigma-Aldrich Company Ltd.) with a complete protease inhibitor cocktail tablet (1
tablet per 50 mL of the buffer; Roche, West Sussex, UK) using a glass pestle. Homogenates
were centrifuged at 2200 x g for 10 min at 4°C and the supernatant representing the
sarcoplasmic pool was aliquoted and stored at -80°C for subsequent western blot analysis. The

54
remaining pellet was washed with 500 μL homogenisation buffer followed by centrifugation
at 700 x g for 10 min at 4°C. Myofibrillar proteins were solubilised in 0.3 M NaOH for 30 min
at 50°C and separated from the insoluble collagen fraction by centrifugation at 10,000 x g for
5 min at 4°C. The remaining supernatant was aliquoted and myofibrillar proteins were
precipitated with 1 M perchloric acid and centrifuged at 700 x g for 10 min at 4°C. The
myofibrillar pellet was washed twice in 1 mL 70% ethanol and hydrolysed in 2 mL 6 M HCl
at 110°C for 24 h. The samples were subsequently dried under a vacuum (SavantTM
SpeedVacTM, ThermoFisher Scientific) and reconstituted in 3 mL 25% acetic acid. Samples
were passed over cation exchange resin columns (100 – 200 mesh; H+ form; Dowex 50WX8;
Sigma-Aldrich Company Ltd.) and eluted with 6 M NH4OH, before being dried under vacuum.
Samples were resuspended in 1 mL distilled water and 1 mL 0.1% formic acid in acetonitrile
and spun at 10,000 x g for 3 min at 4°C. The supernatant was aliquoted, dried under a vacuum
and stored at -20°C.
2.1.11
Isotope ratio mass spectrometry
Enrichment of [2H1]-alanine was determined via isotope ratio mass spectrometry (IRMS). The
bound amino acid extracts were reconstituted in 50 μL N-tert-butyldimethylsilyl-N-
methyltrifluoroacetamide (MTBSTFA) + 1% tert-butyl-dimethylchlorosilane (t-BDMCS) and
50 μL acetonitrile, vortex mixed and heated at 95°C for 40 min in order to derivatise the amino
acids (Molnár-Perl & Katona, 2000). Subsequently, the samples were transferred to a GC vial
and 1 μL was injected into a Delta V Advantage IRMS (ThermoFisher Scientific) fitted with a
Trace 1310 gas chromatograph. Helium was used as the carrier gas with a constant flow of 1
mL∙min-1. The peaks were resolved on a 30 m × 0.25 mm ID × 0.25 μm film DB-5 capillary
column (Agilent Technologies, Santa Clara, CA, USA; temperature program: 110°C for 1 min;

55
10°C∙min-1 ramp to 180°C; 5°C∙min-1 ramp to 220°C; 20°C∙min-1 ramp to 300°C; hold for 2
min). Amino acids eluting from the gas chromatograph were thermally decomposed to their
elemental components using an in-line pyrolysis reactor prior to entry into the IRMS. The
enrichment of tracer was measured by monitoring ion masses 2 and 3 to determine the 2H/1H
ratios of myofibrillar protein-bound [2H]-alanine. A series of known standards were applied to
assess the linearity of the mass spectrometer. Values of MPE were calculated by correcting
against a reference sample, the number of hydrogen atoms added during derivatisation (35
atoms), and by subtracting background plasma enrichment (Wolfe & Chinkes, 2005). It was
assumed that all labelled alanine was present as a singly-labelled species of [2H1]-alanine.
2.1.12
Gas chromatography-mass spectrometry
Enrichment L-[ring-2H5]-phenylalanine, L-[3,3-2H2]-tyrosine and L-[ring-2H4]-tyrosine were
analysed by gas chromatography-mass spectrometry (GC-MS). In order to derivatise the
muscle sample, 50 μL MTBSTFA + 1% t-BDMCS and 50 μL acetonitrile were added to the
amino acid extracts, vortexed, and heated at 95°C for 45 min (Borno, Hulston, & van Hall,
2014). The samples were analysed by GC-MS (7890 GC coupled with a 5975 inert MSD;
Agilent Technologies) in duplicate using electron impact ionisation and selected ion
monitoring for measurement of isotope ratios. One microliter of the sample was injected in
splitless mode (injector temperature: 280°C). Peaks were resolved using an HP5-MS 30 m ×
0.25 mm ID × 0.25 μm capillary column (Agilent Technologies). Helium was used as the
carrier gas at 1.2 mL∙min-1 constant flow rate. The temperature ramp was set from 80–245°C
at 11°C∙min-1, then to 280°C at 40°C∙min-1. For free tyrosine in plasma, mass ratios of m/z 466,
468 and 470 were monitored corresponding to ion fragments m + 0, m + 2 and m + 4,
respectively. For free phenylalanine in plasma, mass ratios of m/z 336 and 341 were monitored

56
corresponding to ion fragments m + 0 and m + 5. For the phenylalanine-bound portion, the
fragments m/z 237 and 239 were monitored corresponding to m + 3 and m + 5. Due to a
concentration-dependent skew in the ion ratios at m/z 237 and 239, enrichments were corrected
against a standard curve of known samples (Calder, Anderson, Grant, McNurlan, & Garlick,
1992; Slater, Preston, McMillan, Falconer, & Fearon, 1995).
2.1.13
Quantitative real-time polymerase chain reactions
In Chapter 4, a series of quantitative real-time polymerase chain reactions (RT-qPCR) were
performed to quantify gene expression. Following the method of Chomczynski and Sacchi
(1987), 23.1 ± 0.2 mg wet weight muscle tissue was weighed out into flat-bottom 2 mL
microcentrifuge tubes (MCT) under liquid N2 and homogenised in 800 μL TRI Reagent
(ThermoFisher Scientific) using a handheld polytron. Batches of up to 4 samples were
homogenised and incubated at room temperature for 5 minutes. Then, 160 μL of 2% iso-amyl
alcohol in chloroform (vol/vol %) was added to each sample and vortexed briefly. These were
incubated at room temperature for a further 2 minutes and centrifuged at 12,000 x g for 15 min
at 4°C. Up to 400 μL of the supernatant was aliquoted into new MCTs and mixed with an equal
volume of ice-cold isopropanol, before being stored at -20°C overnight. The following day,
samples were centrifuged at 12,000 x g for 15 min at 4°C and the supernatant was discarded.
Each pellet was washed in 800 μL 75% ethanol made up in RNase-free water and vortexed to
agitate the pellet. Following a centrifuge at 10,000 x g for 15 min at 4°C, the supernatant was
discarded, and the pellet was re-dissolved in 30 μL of RNase free water. Quantity and quality
of RNA was assessed (NanoDrop Lite Spectrophotometer, ThermoFisher Scientific) using
wavelengths of 260 and 280 nm to ensure concentration above 200 ng·ul-1 and that the ratio of
absorbance at 260 to 280 nm was above 1.8. The mean RNA yield was 9,756 ± 169 ng. First-

57
strand cDNA was synthesised from 2 μg RNA using SuperScript VILO cDNA Synthesis Kit
(Invitrogen, Paisley, UK) by running a single polymerase chain reaction (PCR) cycle (2 min at
4°C, 10 min at 25°C, 60 min at 42°C, 5 min at 85°C, 60 min at 10°C; Alpha Cycler 1, PCRmax,
Staffordshire, UK) and stored at -20°C for subsequent analyses.
To verify the presence of cDNA, a Taqman qPCR assay (ThermoFisher Scientific) for α1 actin
(ACTA1) was performed on every sample. Briefly, reagents were combined in a 96-well mixing
plate. Defrosted cDNA samples were diluted 2-fold using RNase free water and added to the
96-well mixing plate. The mixing plate was vortexed briefly and then transferred to a 384-well
plate in triplicate, such that the final reaction volume in each well was 5 μL. The plate was
sealed and analysed on a QuantStudio 12K Flex qPCR cycler (Applied Biosystems, MA, USA).
All samples were successfully amplified (Ct value <30; n = 285), verifying the presence of
cDNA.
Expression of 224 target genes selected from PubMed literature searches and data from our
laboratory for their roles in amino acid transport, apoptosis, substrate metabolism,
inflammation, insulin signalling, protein synthesis and breakdown, as well as several
transcription factors, were measured by RT-qPCR using 224-format OpenArray qPCR Plates
(ThermoFisher Scientific; full list of analysed genes presented in Appendix 4). Briefly, 1.2 μL
cDNA was combined with OpenArray Master Mix (ThermoFisher Scientific) and RNase free
water up to a final volume of 5 μL in a 384-well plate. Plates were sealed and centrifuged
briefly to ensure mixing of the well contents. An OpenArray Accufill System (Applied
Biosystems) was used to load the OpenArray cards from the 384-well plate (as pictured in
Figure 2.5A), which was manually sealed before being analysed on the QuantStudio 12K Flex
qPCR cycler (Applied Biosystems). Images were obtained of each card and inspected for
correct loading and successful amplification (Figure 2.5C).
58

59
Figure 2.5. (Overleaf) Images from OpenArray RT-qPCR workflow. A: Loading the
OpenArray cards using the Accufill System. A foil-sealed 384-well plate containing cDNA and
PCR reagents is inserted (centre-left). A section of the plate is uncovered, and samples are
automatically loaded on to OpenArray cards (lower right of image). B: example amplification
curve from thermal cycler for a single gene. OpenArray RT-qPCR Analysis Software
automatically detects the cycle threshold (Ct) values. C: Fluorescence image of an OpenArray
card showing correct loading. Each well is automatically loaded with 33 nL from the 384-well
plate containing cDNA and PCR reagents. Incorrect loading or empty wells can be detected by
the absence of fluorescence. D: Fluorescence image after 40 thermal cycles. The intensity of
fluorescence corresponds to amplification and therefore starting amount of cDNA. Each sub-
array containing 8 x 8 wells has a 2 x 2 area in the bottom left and right corners that do not
contain a Taqman gene assay for quality control purposes, thus do not emit fluorescence.
2.2
Principles of isotope tracer methods for measuring protein synthesis
The principal technique used in the studies detailed in this thesis concerns using isotopically-
labelled amino acids to trace rates of protein synthesis in the body. These methods originated
with a series of publications using 15N-labelled tyrosine to show that the protein pool is
continuously turning over (Schoenheimer, Ratner, & Rittenberg, 1939). Subsequently,
numerous methods been developed to quantify rates of protein synthesis and breakdown at the
whole body level or protein subfractions by tracing the kinetics of single amino acids (Wolfe
& Chinkes, 2005). Whilst there are assumptions specific to each method, several general
assumptions apply to the use of stable isotopes, including:
1)
Kinetics of the traced amino acid is representative of the amino acid pool as a whole.
2)
Application of the tracer does not affect the endogenous metabolism of tracee. For
example, a large bolus of [13C]-leucine may enrich the leucine pool but may stimulate
rates of protein synthesis.

60
3)
The tracer is not recycled through synthesis and breakdown.
Whilst not experimentally validated for each experimental chapter, the methods employed in
this thesis are based on previously published and validated approaches and so these
assumptions are not considered to be problematic.
2.2.1
Whole-body protein turnover
The overall rates of protein turnover in the body can determine whether the body is in an
anabolic (i.e., synthesis > breakdown), catabolic (i.e., synthesis < breakdown) or steady (i.e.,
synthesis = breakdown) state. With the use of a single amino acid tracer, whole-body protein
synthesis and breakdown can be calculated using arterialised plasma samples, making this
approach easier to perform and less invasive than other techniques. Following a primed,
continuous, intravenous infusion of the tracer to enrich the plasma free amino acid pool,
reliable data can be collected within 90 min and expressed with respect to well-defined
physiological states (i.e. postabsorptive vs. postprandial periods) (Wolfe & Chinkes, 2005).
Whole-body protein turnover calculations using the tracer dilution principle is based on the
relationship between tracee and tracer over time. Any change in the amount of tracee in the
plasma pool over time will be caused by fluctuations in the rates of appearance (Ra) and
disappearance (Rd) from different sources, as outlined in Figure 2.6.
Once an isotopic equilibrium is reached, enrichment in the plasma amino acid pool will be
dependent on the tracer infusion rate and the total Ra. Thus, Ra is determined from knowledge
of the tracer infusion rate and enrichment in the plasma pool. The total Ra represents the sum
of all processes that contribute to the appearance of a given amino acid in the plasma pool. The
contribution of exogenous amino acids (exogenous Ra) can be quantified by knowing the rate
of tracer infusion and the rate of appearance of amino acids from protein digestion and
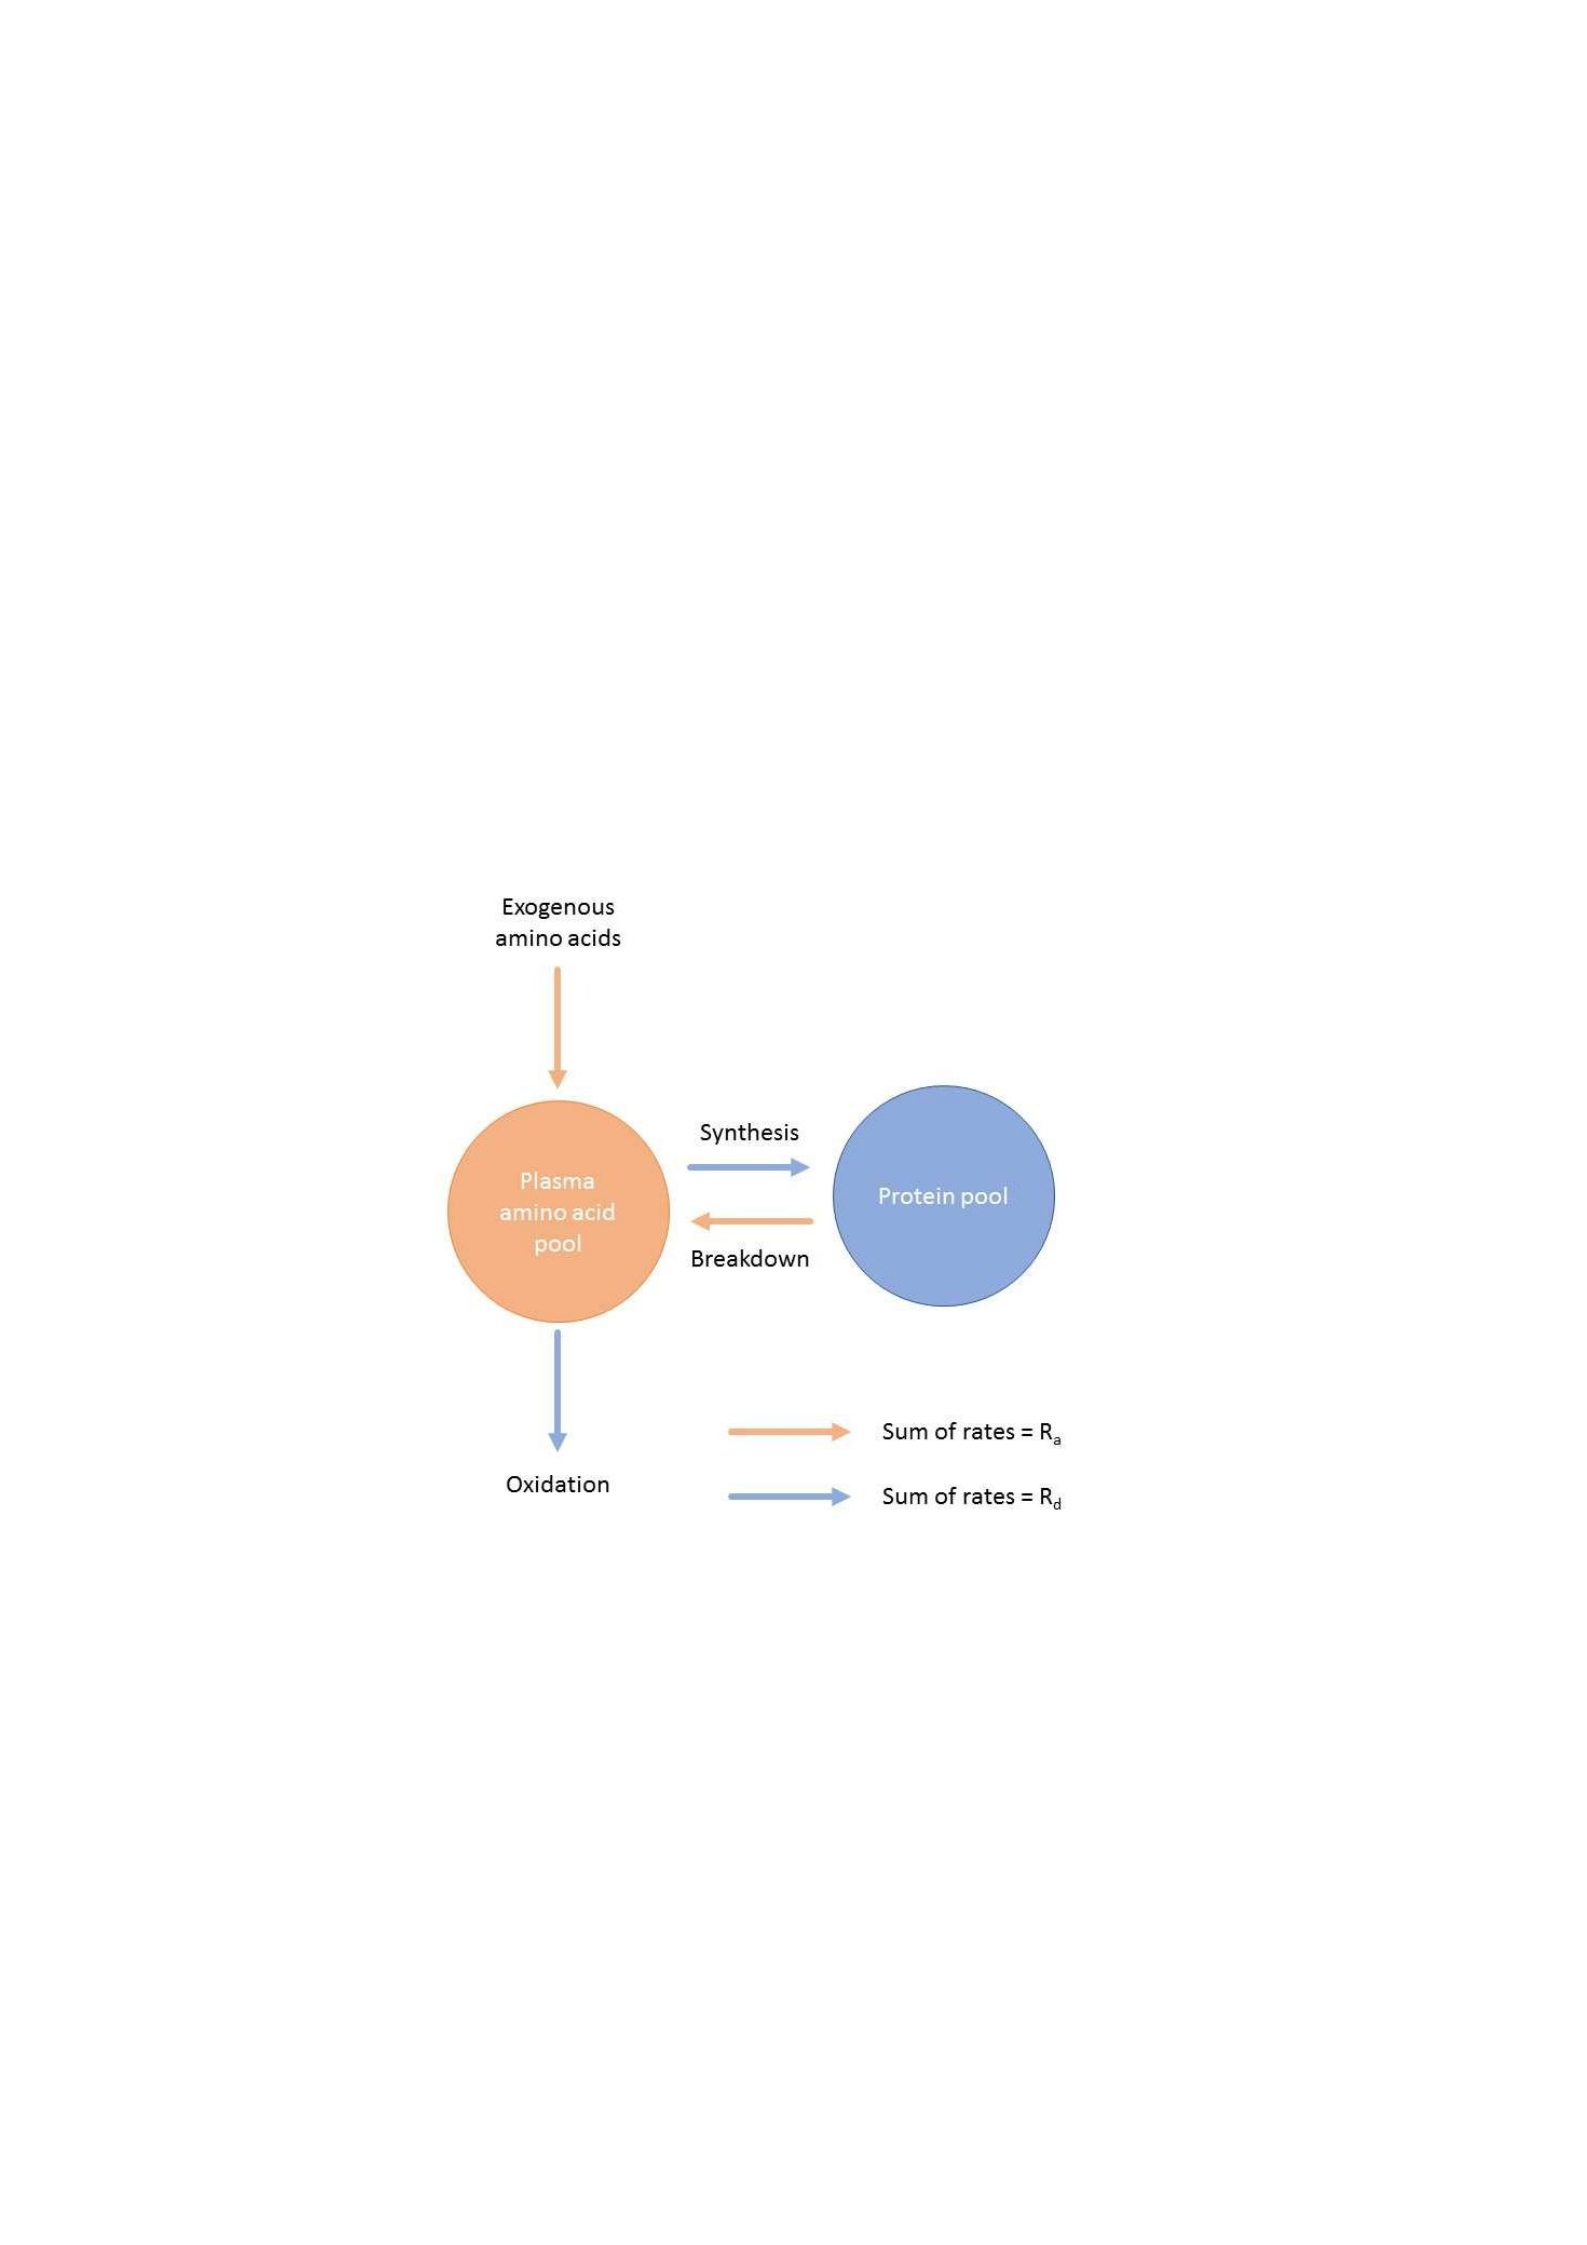
61
absorption. Subtracting exogenous Ra from total Ra is used to obtain endogenous Ra and
represents the sum of endogenous processes releasing amino acids into the plasma pool (Wolfe
& Chinkes, 2005). When using an essential amino acid tracer, endogenous Ra reflects protein
breakdown only under the assumption that the intracellular pool is a single compartment, as
there is no contribution from de novo synthesis. More accurately, this is described as Ra from
protein breakdown.
Figure 2.6. Schematic representation of the determination of whole-body protein synthesis and
breakdown using an essential amino acid tracer. Processes that influence the rate of appearance
(Ra) and disappearance (Rd) shown with orange and blue arrows respectively.

62
The Rd represents amino acids that leave the plasma pool for protein synthesis and oxidation.
In the case of phenylalanine, as used in Chapter 4, a proportion will be hydroxylated into
tyrosine in the liver (Matthews, Marano, & Campbell, 1993). However, with the simultaneous
infusion of a tyrosine tracer, hydroxylation can be accounted for by calculating the total Ra for
tyrosine and the fractional Ra of tyrosine tracer from phenylalanine. By subtracting
hydroxylation rate from total phenylalanine Ra, protein synthesis rate is calculated. Thus,
simultaneous infusion of the amino acid isotopologues [2H5]-phenylalanine and [2H2]-tyrosine
create a validated model in which to study whole-body amino acid kinetics, with the
assumption that phenylalanine kinetics are reflective of the whole amino acid pool (Thompson
et al., 1989).
Using modified Steele equations, the total Ra and Rd can be calculated for substrate kinetics in
the non-steady-state by taking into account the change in pool size over time (Proietto et al.,
1987; Steele, 1959; Wolfe & Chinkes, 2005), which can be used to investigate the effects of
feeding as applied in Chapter 3. Whilst this method was developed for modelling glucose
kinetics, it can be applied to amino acid tracers with an appropriate correction factor to reflect
the fact that the rapidly mixing pool (i.e., plasma) is a fraction of the total free phenylalanine
pool (Engelen, Deutz, Mostert, Wouters, & Schols, 2003; van Loon et al., 2009). However,
with feeding the contribution of dietary amino acids to Ra must be quantified. One approach is
to use an intrinsically labelled protein source, such as [13C]-leucine- or [13C]-phenylalanine-
labelled milk protein produced by intravenously infusing lactating dairy cows (Boirie,
Fauquant, Rulquin, Maubois, & Beaufrere, 1995; van Loon et al., 2009). The appearance of
the tracer in the plasma pool from the ingested protein is used to calculate exogenous Ra, under
the assumption that the appearance of tracer is directly proportional to that of tracee. Plasma
availability following a protein dose similar to that used in Chapters 3 and 4 (~0.3 g·kg body
mass -1) has been estimated to be ~60% (Gorissen et al., 2020). Elsewhere, ~71% of orally

63
ingested amino acids reportedly appear in the plasma following splanchnic extraction in young,
healthy individuals (Volpi et al., 1999).
Alternatively, exogenous Ra may be calculated by taking into account the bioavailability of the
ingested protein (Rennie et al., 1982; Wolfe, Park, Kim, Moughan, & Ferrando, 2020). This is
advantageous when it is not possible to produce an intrinsically labelled protein source, either
due to cost or manufacturing limitations. Furthermore, the accuracy is proposed to be greater
as the intrinsically labelled tracer approach may lead to an underestimation of exogenous Ra
due to amino acid kinetics in the splanchnic bed, resulting in a subsequent overestimation of
protein breakdown (Wolfe et al., 2020; Wolfe et al., 2019). The estimation of bioavailability
requires knowledge of three factors: 1) amount of tracee provided in the nutritional
intervention; 2) true ileal digestibility of tracee; 3) clearance of tracee from the splanchnic bed.
Although true ileal digestibility cannot be determined with ease, data from human, pig and
rodent studies indicate that phenylalanine digestibility is 96%, with no differences between
intact or hydrolysed casein sources (Deglaire & Moughan, 2012). Subsequently, tracee may be
cleared from the splanchnic bed through either net uptake for protein synthesis or
hydroxylation. Whilst equivocal data exist describing the splanchnic protein synthesis and
breakdown response to feeding (Bouteloup-Demange, Boirie, Dechelotte, Gachon, &
Beaufrere, 1998; Coeffier et al., 2013), the size and turnover rate these protein pools is argued
not to induce considerable error (<~5%) should this process be ignored (Wolfe et al., 2020).
Finally, hydroxylation of tracee (specifically phenylalanine) can be calculated by the difference
between phenylalanine hydroxylation rates in the postprandial versus postabsorptive state
(Wolfe et al., 2020).
2.2.2
Muscle protein synthesis with continuous intravenous infusion

64
𝑡1
Stable isotopes can also be used to measure synthesis rates of specific proteins using the tracer
incorporation principle. This approach is more invasive than measurements at the whole-body
level if specific tissues are targeted, such as muscle.
The fractional synthetic rate (FSR), which represents the fraction of the total protein pool that
is synthesised over time, is calculated using the precursor-product method (Wolfe & Chinkes,
2005). To obtain FSR, the rate of incorporation into the protein pool (product) is then divided
by precursor enrichment. This is represented by:
𝐹𝑆𝑅 = 𝐸𝐵(𝑡2)− 𝐸𝐵(𝑡1)
∫
𝑡2
𝐸
𝑃
(𝑡)𝑑𝑡
(2.1)
Where EB and EP represent muscle protein (product) and precursor enrichment, respectively,
at a given time point (t).
Enrichment of the precursor pool can be achieved via continuous intravenous infusion of a
labelled amino acid, such as [13C1]-leucine or [2H5]-phenylalanine. This is well-suited to a
laboratory environment and therefore extraneous factors that may modulate protein metabolism
such as diet or exercise can be controlled for. As with the tracer dilution principle for measuring
whole-body protein turnover, a primed continuous infusion will reach a steady-state of
precursor enrichment in 90-120 minutes after which time FSR values can be obtained (Wolfe
& Chinkes, 2005). Given that variability in FSR is reduced with greater differences in product
enrichment between samples (Smith, Patterson, & Mittendorfer, 2011), a high infusion rate is
theoretically advantageous for calculating FSR. Furthermore, this will allow FSR to be
calculated over shorter time frames, increasing the likelihood that the rate of tracer
incorporation is constant. Nonetheless, a large infusion rate may stimulate protein synthesis

65
and invalidate the assumption that tracer provision will not alter endogenous metabolism
(Smith, Reynolds, Downie, Patel, & Rennie, 1998). In practice, an infusion rate to achieve a
target enrichment of ~7% MPE is desirable (Wolfe & Chinkes, 2005).
Following steady-state enrichment of the precursor pool, product enrichment rises
exponentially to a plateau equal to the enrichment of the true precursor. For a slowly turning
over protein pool such as muscle, it is impractical to wait until a true plateau is achieved in
order to obtain a value for precursor enrichment, and so a pool representative of the true
precursor can be used instead (Wolfe & Chinkes, 2005). Theoretically, the transfer RNA
(tRNA) pool is a good representation as amino acids are bound to tRNA prior to synthesis into
proteins. However, isolation of the tRNA pool is technically challenging and requires a muscle
sample larger than that obtained during a typical muscle biopsy (~20 g, using GC-MS
methodology) (Baumann, Stirewalt, O'Rourke, Howard, & Nair, 1994). Therefore, alternative
precursors are commonly used, and the suitability can be informed from animal models. In pigs
that were intravenously infused with [13C1]-leucine and [2H5]-phenylalanine, tissue fluid
enrichment (comprised of ~80% intracellular fluid) was greater than the tRNA pool only with
leucine (~26%), whereas phenylalanine enrichment was in agreement between the two pools
(Baumann et al., 1994). In the same study, arterial enrichments exceeded that of tRNA by ~45%
suggesting that tissue fluid enrichment is an appropriate surrogate for the precursor pool.
Accordingly, in a recent metanalysis of 71 studies employing primed, constant tracer amino
acid infusions, mixed muscle FSR values were significantly higher when using the intracellular
or tissue fluid vs. plasma free amino acid enrichment (Smith et al., 2011). Nonetheless,
variability in FSR calculated using either precursor pool was similarly small, suggesting that
either precursor is an appropriate choice when comparing experimental conditions.

66
2.2.3
Deuterated water ingestion
For the determination of MPS rates in “free-living” conditions, outside of a laboratory, an
alternative method involving deuterium oxide (2H2O) has recently been developed (Dufner et
al., 2005; Gasier, Fluckey, & Previs, 2010; MacDonald et al., 2013). Enrichment of the
precursor pools can be achieved by oral ingestion of a 2H2O bolus, negating the requirement
for intravenous infusion. After rapid equilibrium with the body water pool, endogenous
labelling of alanine occurs via transamination (Oshima & Tamiya, 1961), which is then
incorporated into newly synthesised muscle proteins (Figure 2.7). If the body water pool
remains appropriately enriched, muscle protein synthesis rates can be expressed over hours,
days or weeks. Depending on the time frame used, the assumption of a constant rate of tracer
infusion is adjusted such that the calculated FSR represents an average or cumulative rate of
protein synthesis. Thus, the use of orally ingested 2H2O is beneficial to situations where longer-
term (i.e., daily, rather than hourly) measures of FSR are required.
Figure 2.7. Schematic of how oral consumption of 2H2O can be used to measure rates of muscle
protein synthesis. Following 2H2O consumption, deuterium rapidly equilibrates with the body
water pool. Alanine is labelled through deuterium-hydrogen exchange during transamination
reactions, which is then bound to tRNA before being incorporated into muscle proteins.
Adapted from (Gasier et al., 2010).

67
In addition to the benefits of measuring FSR over longer periods of time, lower precursor
enrichments can be used as gas chromatography/pyrolysis/isotope ratio–mass spectrometry
(GC/P/IRMS) systems can detect very low (>0.002% atom per cent excess; APE) levels of
label incorporation (MacDonald et al., 2013; Voogt et al., 2007). However, there is no clear
consensus on the optimal dosing strategy to achieve the desired enrichment in humans, which
is typically ~0.1 – 0.8% APE (Bell, Seguin, Parise, Baker, & Phillips, 2015; Brook et al., 2015;
Damas et al., 2016b; Davies et al., 2020; Holwerda et al., 2018; Kilroe et al., 2020; MacDonald
et al., 2013; Robinson, Turner, Hellerstein, Hamilton, & Miller, 2011; Scalzo et al., 2014;
Wilkinson et al., 2015; Wilkinson et al., 2014). A ‘loading day’ is often employed, whereby a
2H2O bolus is separated into smaller aliquots to be consumed every ~30-90 min to minimise
the chances of experiencing nausea and vertigo (Gasier et al., 2010). Thereafter, additional
daily or weekly doses may be provided to keep body water enrichment in a steady-state (Bell
et al., 2015; Brook et al., 2015; Holwerda et al., 2018; Kilroe et al., 2020; Robinson et al., 2011;
Scalzo et al., 2014), although this is not always the case. Given that FSR calculated using 2H2O
is considered to be an average of all periods of protein synthesis, a steady-state must be
maintained such that the change in product enrichment is reflective of the true rates of muscle
protein synthesis, rather than differences in precursor enrichment. That is, the difference in
product enrichment between two time points will be greater if the true rates of MPS are elevated
early in the measurement window when precursor enrichment is highest than if MPS rates are
elevated later in the window when precursor enrichment is lowest. This could potentially lead
to an over- or under-estimation of the true rates of MPS, respectively. Further sources of error
are introduced when the fall in precursor enrichment is assumed to be linear over time; the loss
of precursor will be a product of its turnover rate and therefore will follow first-order kinetics
(MacDonald et al., 2013). Assuming otherwise will overestimate the mean precursor pool
enrichment and subsequently underestimate FSR. An additional consideration is that the

68
labelling of the product is directly dependant on the enrichment of the body water pool (Busch
et al., 2006). Assuming that the probability of enrichment at each carbon-hydrogen bond is
approximately equal to the enrichment of body water (Previs et al., 2004), 99.1% of enriched
alanine will exist as [2H1]-alanine at 0.6% APE body water (Busch et al., 2006). The remaining
proportion will exist as increasingly smaller quantities of doubly-, triply-, and quadruply-
labelled species. However, if body water enrichment rises to 0.8% APE, 98.7% of enriched
alanine will be [2H1]-alanine and ~77% more deuterium will be present on the growing
proportions of multiply-labelled species. As MPE calculations from GC/P/IRMS and precursor
pool measurements assume that alanine is a singly labelled species, this skew will overestimate
the true enrichment of [2H1]-alanine.
In practice, the relatively slow turnover rates of both precursor and product pools mean that
considerable error is unlikely to be introduced if the sampling time is relatively short (i.e.,
several days, rather than weeks). However, due to the multiple sources of variability when
measuring FSR (Smith et al., 2011), maintaining steady-state may improve statistical power
and increase the validity of the associated assumptions.
Recently, Holwerda et al. (2018) provided 8 x 50 mL of 70% 2H2O to achieve a body water
enrichment of ~0.62% in healthy young males. Daily maintenance doses of 50 mL were
provided and although enrichment increased numerically to ~0.73% after 7 days, this not
significant. Using an identical dosing protocol, Kilroe et al. (2020) achieved 0.69% body water
enrichment initially, with enrichment rising significantly to 0.83% after 7 days. This is likely
due to the differing body mass between the two studies (~78 kg versus ~74 kg, respectively),
as body mass is directly proportional to the total body water pool size in young, lean, healthy
individuals (Watson, Watson, & Batt, 1980). Indeed, correcting dosage for body weight
achieves a reproduceable target enrichment across healthy individuals ranging from 51 – 108
kg body mass, although in this instance a steady state was not attempted (Wang et al., 2014).

69
Based on these data, we present a novel dosing strategy to achieve and maintain the target
body water enrichment:
𝐷
𝐿𝑜𝑎𝑑𝑖𝑛g
(𝑚𝑙
∙
𝑘𝑔
−1
)
=
𝑝𝑀
×𝐸
𝑇𝑎r𝘨𝑒𝑡
𝐸
0r𝑎𝑙
× 1000 (2.2)
𝐷𝑀𝑎𝑖𝑛𝑡𝑒𝑛𝑎𝑛𝑐𝑒 (𝑚𝑙 ∙ 𝑘𝑔−1 ∙ 𝑑−1) = 𝐷𝐿𝑜𝑎𝑑𝑖𝑛g × 𝑇 (2.3)
Where the total loading dose required (DLoading) is calculated from the fraction of body mass
that is comprised of body water (pM), the desired body water enrichment (ETarget) and the
enrichment of 2H2O consumed (EOral). The daily maintenance dose (DMaintenance) is calculated
from DLoading multiplied by the daily turnover rate of the body water pool (T). Figure 2.8
displays the resultant plasma 2H enrichment using this modified dosing strategy from studies
presented in Chapters 4 and 5, under the assumption that the body water pool contributes 70%
body mass in healthy lean individuals (Watson et al., 1980) and turns over at 9 %·d-1
(Shimamoto & Komiya, 2000). Mean daily plasma enrichment using this approach was 0.63%
APE, with no significant changes over time.
When using 2H2O to calculate FSR, plasma or intracellular [2H]-alanine can be used as a
surrogate precursor pool. Furthermore, body water enrichment may be used with an appropriate
correction factor as plasma [2H1]-alanine is ~3.7-fold greater than body water, with
enrichments between the two pools correlating closely within individuals (Holwerda et al.,
2018; Kilroe et al., 2020; MacDonald et al., 2013; Wilkinson et al., 2014). Accordingly, FSR
calculated using either the body water or plasma [2H1]-alanine pool as a surrogate precursor
strongly agree (Kilroe et al., 2020). Furthermore, despite being several steps removed from the
true precursor pool, FSR calculated using body water enrichment is very similar to that
calculated with an intravenous infusion of [13C6]-phenylalanine (Wilkinson et al., 2015),
validating its use to calculate FSR. Thus, using body water enrichment as a surrogate for

70
1.0
0.8
0.6
0.4
0.2
0.0
Day 2
Day 4
precursor enrichment may be advantageous due to tissue limitations and the fewer analytical
steps required.
Figure 2.8 Daily plasma 2H enrichment (%) following 2H2O consumption from studies
presented in Chapter 4 (A) and Chapter 5 (B). The dosing protocol used was modified from
previous work (Holwerda et al., 2018; Kilroe et al., 2020) and designed to achieve 0.6%
enrichment with single loading day (Day 0), followed by daily maintenance doses to achieve a
steady-state. A: No main effect of time (P = 0.75) as assessed by a repeated measures one-way
ANOVA. B: No significant difference in enrichment between day 2 and 4 (P = 0.79) as assessed
by a paired t-test.
Plasma 2H enrichment (%)

71
Chapter 3 - Characterising the Whole-Body and Muscle Protein Metabolic
Response to Protein-Polyphenol Ingestion.

72
3.1
Abstract
Existing research indicates that protein ingestion increases whole-body protein balance and
myofibrillar protein synthesis (MyoPS), the duration of which is determined by the exogenous
amino acid availability. Mixed protein blends may prolong aminoacidaemia; however, the
absence of non-nitrogenous controls mean that the relationship between MyoPS and exogenous
amino acids per se is unclear. Twenty healthy, recreationally active, volunteers (age: 22 ± 1 y;
body mass: 67 ± 3 kg; BMI: 22.6 ± 0.5 kg·m-2) consumed either 20 g protein from a blend of
whey, casein, and pea, and 650 mg pomegranate extract (PPB; n = 10; 5 females) or an
isocaloric carbohydrate placebo (PLA; n =10; 5 females) during 8.5 h of intravenous L-[ring-
2H5]-phenylalanine and L-[3,3-2H2]-tyrosine infusion. Arterialised blood samples and muscle
biopsies were collected to calculate basal and postprandial whole-body protein turnover and
myofibrillar fractional synthetic rates (FSR). PPB consumption increased postprandial plasma
amino acid concentration (P < 0.001) and induced positive net protein balance (P < 0.001)
versus PLA. Myofibrillar FSR increased from 0.019 ± 0.007 and 0.013 ± 0.003 %·h-1 during
the basal period to 0.028 ± 0.006 and 0.026 ± 0.003 %·h-1 following consumption of PLA and
PPB respectively (P < 0.05). However, myofibrillar FSR was similar between PLA and PPB
at all timepoints. The present results indicate that PPB feeding creates an anabolic milieu versus
carbohydrate placebo. Whether exogenous amino acids per se determine the myofibrillar
protein synthetic response requires further work.

73
3.2
Introduction
Protein turnover is highly responsive to feeding in healthy, young adults, stimulating protein
synthesis and suppressing breakdown (Burd, Gorissen, van Vliet, Snijders, & van Loon, 2015;
Kim et al., 2016; Rennie et al., 1982; Volpi et al., 1999). At the whole-body level, amino acid
clearance from plasma increases ~30% with feeding (Boirie et al., 1996; Burd et al., 2015;
Gorissen et al., 2014; Rennie et al., 1982). Conversely, inward transport and incorporation into
protein within skeletal muscle increase approximately two-fold (Burd et al., 2015; Gorissen et
al., 2014; Rennie et al., 1982; Volpi et al., 1999), indicating a preferential shift in amino acid
delivery and uptake toward the muscle from basal conditions. From a mechanistic standpoint,
pronounced elevations in systemic insulin increase peripheral blood flow (Bennet, Connacher,
Scrimgeour, Jung, & Rennie, 1990; Timmerman et al., 2010), although this may not be a
prerequisite of increased amino acid uptake as ~two-fold greater delivery and uptake in the
muscle has been observed with feeding despite no measurable change in blood flow (Volpi et
al., 1999). Nonetheless, the resultant rise in amino acid availability to the muscle stimulates
rates of muscle protein synthesis (Biolo, Declan Fleming, & Wolfe, 1995a; Greenhaff et al.,
2008; Timmerman et al., 2010); the reverse is true also, as the muscle protein synthetic response
is attenuated if amino acid availability is not maintained (Tessari et al., 1986). Indeed, in the
absence of exogenous amino acid provision, systemic insulinaemia restricts amino acid
availability through suppressing the plasma appearance of those derived from protein
breakdown (Borsheim et al., 2004b; Gelfand & Barrett, 1987; Tessari et al., 1986). Moreover,
pharmacological strategies to reduce blood flow (Timmerman et al., 2010), as well as post-
exercise cold-water immersion (Fuchs et al., 2020), reduce rates of muscle protein synthesis by
~35% and ~20% respectively, regardless of systemic amino acid concentrations, highlighting
the role of amino acid availability and delivery in determining protein synthesis rates. Given
that the role of exogenous amino acid availability in promoting recovery and hypertrophy will

74
be explored in Chapters 4 and 5, respectively, it is firstly imperative to characterise whole body
and muscle protein metabolism with nutritional intervention.
A dose-response relationship exists whereby mixed-muscle and myofibrillar protein synthesis
(MyoPS) increases linearly, by ~93% and ~49% respectively, with up to 20 g of protein
ingestion (Moore et al., 2009a; Witard et al., 2014). However, several studies have
demonstrated equal initial stimulation of MyoPS lasting 1.5 - 3 h with optimal (i.e., 25 – 30 g
milk protein containing 3 g leucine ) and suboptimal doses of protein (6 - 12 g total protein
and/or amino acids from varying combinations of whey and branched-chain, essential and non-
essential amino acids), regardless of the extent of insulinaemia and aminoacidaemia
(Churchward-Venne et al., 2014; Churchward-Venne et al., 2012; Fuchs et al., 2019). Together,
these data suggest that amino acid provision of any quantity initially stimulates rates of MyoPS,
the duration of which is dictated by the availability of amino acids. Nonetheless, stimulation
has been observed by some to be refractory after 90 – 120 min despite elevated amino acid
availability (Atherton et al., 2010a; Bohe, Low, Wolfe, & Rennie, 2001), whilst others
demonstrate that ingesting more complete protein or amino acid boluses (Churchward-Venne
et al., 2014; Churchward-Venne et al., 2012; Fuchs et al., 2019), repeated protein feedings
(Mitchell et al., 2015) and blends of fast and slow-digesting proteins (Holm et al., 2010; van
Vliet et al., 2019) result in prolonged aminoacidaemia and sustained stimulation of MyoPS
between 120 – 300 min following consumption. The relationship between exogenous amino
acid availability and MyoPS is therefore unclear. Moreover, few studies compare exogenous
amino acid provision to an isocaloric control; in older males, MyoPS assessed by either [15N]-
phenylalanine (Reitelseder et al., 2019) or L-[ring-13C6]-phenylalanine (Agergaard et al., 2017)
tracers increased ~43% after either whey, casein or carbohydrate consumption, suggesting that
feeding-related factors other than exogenous amino acid availability may stimulate myofibrillar
protein synthesis. However, in these instances, age-related differences in protein absorption

75
and metabolism may have impaired the muscle’s sensitivity to protein ingestion (Katsanos,
Kobayashi, Sheffield-Moore, Aarsland, & Wolfe, 2005; Volpi et al., 1999; Wall et al., 2015).
To our knowledge, no study to date has compared the effect of amino acid provision to a non-
nitrogenous, isocaloric control in healthy young individuals. As such, whether stimulation of
MyoPS is caused by exogenous amino acids per se requires further attention.
This study investigated the anabolic response to consumption of a 20 g mixed protein blend
targeted at increasing and sustaining amino acid availability, versus isocaloric carbohydrate
placebo. A dual-tracer approach was used to assess whole-body protein turnover rates as well
as rates of myofibrillar protein synthesis prior to and throughout a 5 h postprandial period. It
was hypothesised that nutritional intervention would cause prolonged aminoacidaemia and
elevate rates of myofibrillar protein synthesis at both early (0-2 h) and late (2-5 h) time points
versus isocaloric placebo.
3.3
Methods
3.3.1
Participants
Twenty healthy, recreationally active participants (10 male, 10 female; age: 22 ± 1 y; body
mass 67 ± 3 kg; BMI 22.6 ± 0.5 kg·m-2) volunteered to take part in this study. The sample size
was calculated a priori assuming that 20 g protein stimulates muscle protein synthesis by 75%
at rest in healthy, young individuals (Wall et al., 2015), and that carbohydrate will not stimulate
rates of protein synthesis above postabsorptive levels. Using previously published data using a
similar methodologies (Wall et al., 2015), we expect an effect size of 1.39. With 80% power at
α = 0.05 using a paired t-test, this effect size should be detectable in 10 subjects. Prior to
inclusion, participants attended the laboratory for routine medical screening to ensure they did
not contravene the following exclusion criteria: diagnosed metabolic impairment (e.g., type 1

76
or type 2 diabetes); cardiovascular disease; hypertensive (≥140/90 mmHg); chronic use of
prescribed or over-the-counter pharmaceuticals; personal or family history of epilepsy,
schizophrenia or seizures; the presence of an ulcer in the stomach or gut; pre-existing condition
with liver or kidneys; regular use of nutritional supplements; and/or an allergy to milk,
lidocaine or amino acids. Written consent was obtained from all participants following the
explanation of the experimental procedures, which were approved by the University of Exeter’s
Sport and Health Sciences Ethics Committee. This study was registered as a clinical trial with
ClinicalTrials.gov (NCT03571425).
Table 3.1. Subject characteristics.
PLA
PPB
(n = 10)
(n = 10)
Sex (male:female)
5:5
5:5
Age (y)
22 ± 1
21 ± 0
Body mass (kg)
67.1 ± 3.3
67.6 ± 4.3
Height (cm)
171 ± 3
173 ± 4
BMI (kg·m-2)
22.8 ± 0.8
22.4 ± 0.6
Body fat (% body mass)
15 ± 2
15 ± 3
Lean mass (kg)
57.0 ± 2.8
57.0 ± 3.9
Energy (MJ·d−1)
9.6 ± 1.4
7.9 ± 1.0
Protein (g·d−1)
97 ± 16
85 ± 10
Protein (g·kg−1·d−1)
1.5 ± 0.2
1.3 ± 0.1
Values represent mean ± SEM. PLA, carbohydrate placebo treatment; PPB, protein-polyphenol
treatment; BMI, body mass index. Energy and protein values are habitual dietary intake. All
between treatment comparisons P > 0.05.

77
3.3.2
Experimental protocol
Following inclusion, participants were randomly assigned to one of two groups in a double-blind,
placebo-controlled, parallel-group design, counter-balanced for gender. After consuming a
standardised diet on the evening prior (976 kcal, 38.4% energy (% En) carbohydrate, 16.8% En
protein, 44.8% En fat), participants arrived in the laboratory at 0800 following a ≥10 h fast. A
schematic of the experimental trial is shown in Figure 3.1. Participants rested in a semi-supine
position whilst a Venflon cannula was inserted anterograde into an antecubital vein of one arm for
stable isotope infusion. An initial blood sample was taken to measure background isotope
enrichment (t = -210 min), after which the plasma phenylalanine and tyrosine pools were primed
with 2.94 μmol·kg-1 L-[ring-2H5]-phenylalanine and 1.04 μmol·kg-1 L-[3,3-2H2]-tyrosine.
Continuous infusion of 0.049 μmol·kg-1·min-1 L-[ring-2H5]-phenylalanine and 0.017 μmol·kg-
1·min-1 L-[ring-3,5-2H2]-tyrosine began thereafter and was maintained over the experimental trial
(8.5 h).
A second Venflon cannula was inserted retrograde into a heated, dorsal hand vein and kept patent
with a 0.9% saline infusion. The hand was placed in a heated hand warmer at 55°C for arterialised
venous blood sampling (Abumrad, Rabin, Diamond, & Lacy, 1981), which was collected at t = -
120, -60, 0, 15, 30, 45, 60, 90, 120, 150, 180, 240 and 300 min. Muscle biopsies were collected at
t = -120 and 0 from a randomly assigned leg (counter-balanced for leg dominance) for the
calculation of basal myofibrillar protein synthesis rates. Immediately after the second biopsy, a 3
min period began whereby participants consumed their allocated experimental beverage. An
additional 50 mL water was used to rinse the beverage containers and then consumed by
participants. Further muscle biopsies were obtained at t = 120 and 300 from the contralateral leg
for the calculation of postprandial myofibrillar protein synthesis rates.

78
Figure 3.1. Graphical representation of the experimental protocol.
3.3.3
Experimental beverages
A commercially available protein-polyphenol supplement (Beachbody LLC, Santa Monica,
CA, USA) was consumed by participants in PPB, which contained 20 g total protein from a
blend of whey, pea and casein proteins, 10 g carbohydrate and 650 mg pomegranate extract
(211 mg polyphenols). Participants in the PLA group received a taste- and colour-matched,
isocaloric, maltodextrin placebo (30 g carbohydrate). A full breakdown of macronutrient,
amino acid composition and polyphenol content is displayed in Appendix 2. Beverages were
made up to 225 mL in water following the addition of 1500 mg powdered acetaminophen
(paracetamol) in order to measure postprandial gastric emptying rates (Glerup et al., 2007), as
the appearance of exogenous amino acids is initially limited by gastric emptying and absorption
in the gastrointestinal tract (Holwerda et al., 2017). A separate researcher made up the beverages
in order to maintain double-blinding for the researcher providing the beverages.
3.3.4
Blood sample collection and analyses
One aliquot of every blood sample (0.5 mL) was collected in a fluoride/oxalate tube
(Vacutainer®, BD Company, Franklin Lakes, NJ, USA) rolled for 2 minutes to inhibit
glycolysis and then analysed for whole blood glucose concentrations (YSI 2300 PLUS, Yellow

79
Springs, OH, USA). A second aliquot (3 mL) was collected in a serum separator tube
(Vacutainer®, BD company) and left to clot at room temperature for ≥30 min. A third aliquot
(3 mL) was collected in a lithium heparin container (Vacutainer®, BD company) and processed
immediately. Serum separator and lithium heparin tubes were centrifuged at 2850 x g for 10
min at 4°C to obtain serum and plasma samples, respectively, which were aliquoted and snap-
frozen liquid nitrogen prior to storage at -80°C for further analysis.
Arterialised serum samples were used to determine insulin (Human insulin ELISA kit EIA-
2935, Oxford Biosystems Ltd, Oxfordshire, UK) and paracetamol concentrations (Paracetamol
Assay Kit K8002, Cambridge Life Sciences Ltd, Cambridgeshire, UK).
Enrichment of L-[ring-2H5]-phenylalanine, L-[3,3-2H2]-tyrosine and L-[ring-2H4]-tyrosine, and
concentration of phenylalanine, tyrosine, leucine, isoleucine and valine were determined as
described in Chapter 2. Briefly, arterialised plasma samples were deproteinised on ice with an
equal volume of 15% 5-sulfosalicylic acid, prior to centrifugation at 4000 x g for 10 min at
4°C. Supernatants were passed over cation exchange resin columns (100 – 200 mesh; H+ form;
Dowex 50WX8; Sigma-Aldrich Company Ltd., Dorset, UK) with 6 mL of 0.5 M acetic acid.
Amino acids were eluted with 6 M NH4OH and dried under a vacuum for 8 h at 60°C (SavantTM
SpeedVacTM, ThermoFisher Scientific, Waltham, MA, USA).
Following derivatisation to tert-butyl-dimethylsilyl (TBDMS) esters, amino acid enrichments
were determined using electron impact ionisation by monitoring labelled and unlabelled ions
at mass/charge (m/z) of 341 and 336 for L-[ring-2H5]-phenylalanine, 468 and 466 for L-[3,3-
2H2]-tyrosine, and 470 and 466 for L-[ring-2H4]-tyrosine. Amino acid concentrations were
calculated from the mass charge corresponding to the unlabelled ion against a standard curve
of known concentrations. Samples from one participant in each group were re-extracted with

80
10 μL of 2 mM norleucine to calculate extraction efficiency, to which all other samples were
corrected (see Chapter 2 for more details).
3.3.5
Muscle biopsy collection and analyses
Muscle biopsy samples were obtained as described in Chapter 2. Briefly, samples were
collected under local anaesthesia (2% lidocaine) by the Bergström needle technique modified
for suction (Tarnopolsky et al., 2011) from the mid-section of the m. vastus lateralis
approximately 15 cm proximal from the knee. All samples were rapidly dissected of visible fat
and connective tissue, frozen in liquid-nitrogen-cooled isopentane and stored at -80°C until
subsequent analysis.
Myofibrillar protein fractions were isolated as described in Chapter 2. Briefly, ~50 mg wet
weight muscle tissue was homogenised using a glass pestle in 7.5 μL·mg-1 ice-cold
homogenisation buffer (50 mM Tris·HCl pH 7.4, 1 mM EDTA, 1 mM EGTA, 10 mM β-
glycerophosphate salt, 50 mM NaF and 0.5 mM activated Na3VO4; Sigma-Aldrich Company
Ltd., Dorset, UK) with a cOmplete protease inhibitor cocktail tablet (Roche, West Sussex, UK).
Following centrifugation, the pellet was washed with homogenisation buffer and the
myofibrillar proteins were solubilised in 0.3 M NaOH for 30 min at 50°C. The insoluble
collagen fraction was separated by centrifugation and myofibrillar proteins were precipitated
with 1 M perchloric acid. The myofibrillar pellet was washed twice in 1 mL 70% ethanol and
hydrolysed in 2 mL 6 M HCl at 110°C for 24 h, before being dried under a vacuum (SavantTM
SpeedVacTM, ThermoFisher Scientific). The samples were reconstituted in 25% acetic acid and
eluted from cation exchange resin columns (100 – 200 mesh; H+ form; Dowex 50WX8; Sigma-
Aldrich Company Ltd) with 6 M NH4OH. Samples were dried under vacuum prior to being
suspended in 1 mL distilled water with 1 mL 0.1% formic acid in acetonitrile and spun at

81
10,000 x g for 3 min at 4°C. The resultant supernatant was aliquoted, dried under a vacuum
and stored at -20°C.
Samples were converted to their tert-butyl-dimethylsilyl (TBDMS) derivatives as described in
Chapter 2. The myofibrillar protein-bound amino acid phenylalanine enrichments were
determined using electron impact ionisation by monitoring mass/charge (m/z) of 239 and 237.
Standard curves were applied from a series of known standard enrichment values against the
measured values in order to correct for any concentration dependant shift in the measured
labelled to unlabelled m/z ratios.
3.3.6
Calculations
The fractional synthetic rate of myofibrillar proteins (myoFSR) was calculated using the
following precursor-product equation (Wolfe & Chinkes, 2005):
𝑚𝑦𝑜FSR (%·h-1) = Em2 – Em1
Ep × (𝑡1−𝑡2) × 100% (3.1)
Where (Em2 - Em1) is the increase in myofibrillar protein-bound L-[ring-2H5]-phenylalanine
enrichment from t1 to t2 and Ep is the mean precursor enrichment between t1 and t2.
Whole-body phenylalanine kinetics were calculated from plasma enrichment of L-[ring-2H5]-
phenylalanine, L-[3,3-2H2]-tyrosine, and L-[ring-2H4]-tyrosine, using the following
calculations (Kim et al., 2016; Wolfe & Chinkes, 2005):

82
𝑎
𝑑𝑡
𝑑
𝑎
𝑇𝑜𝑡𝑎𝑙 𝑟𝑎𝑡𝑒 𝑜𝑓 𝑎𝑝𝑝𝑒𝑎𝑟𝑎𝑛𝑐𝑒 𝑖𝑛𝑡𝑜 𝑝𝑙𝑎𝑠𝑚𝑎 (𝑅 ) = 𝐹
𝐸 (3.2)
𝐹𝑟𝑎𝑐𝑡𝑖𝑜𝑛𝑎𝑙 𝑅𝑎
𝑜𝑓
𝑇𝑦𝑟
𝑓𝑟𝑜𝑚
𝑃ℎ𝑒
=
𝐸
𝑇𝑦r
𝑀+4
𝐸
𝑃ℎ𝑒
𝑀+5
(3.3)
𝑃ℎ𝑒 ℎ𝑦𝑑𝑟𝑜𝑥𝑦𝑙𝑎𝑡𝑖𝑜𝑛 𝑟𝑎𝑡𝑒 = 𝑓𝑟𝑎𝑐𝑡𝑖𝑜𝑛𝑎𝑙 𝑅𝑎 𝑜𝑓 𝑇𝑦𝑟 𝑓𝑟𝑜𝑚 𝑃ℎ𝑒 × 𝑇𝑦𝑟 𝑅𝑎 (3.4)
𝑃𝑟𝑜𝑡𝑒𝑖𝑛 𝑠𝑦𝑛𝑡ℎ𝑒𝑠𝑖𝑠 𝑟𝑎𝑡𝑒 (𝑃𝑆) = 𝑃ℎ𝑒 𝑅𝑎 − 𝑃ℎ𝑒 ℎ𝑦𝑑𝑟𝑜𝑥𝑦𝑙𝑎𝑡𝑖𝑜𝑛 𝑟𝑎𝑡𝑒 (3.5)
𝑃𝑟𝑜𝑡𝑒𝑖𝑛 𝑏𝑟𝑒𝑎𝑘𝑑𝑜w𝑛 𝑟𝑎𝑡𝑒 (𝑃𝐵) = 𝑃ℎ𝑒 𝑅𝑎 − 𝐹𝑃ℎ𝑒 − 𝐸𝑥𝑜𝑔𝑒𝑛𝑜𝑢𝑠 𝑃ℎ𝑒 𝑅𝑎 (3.6)
𝑁𝑒𝑡 𝑝𝑟𝑜𝑡𝑒𝑖𝑛 𝑏𝑎𝑙𝑎𝑛𝑐𝑒 = 𝑃𝑆 − 𝑃𝐵 (3.7)
Where for a given amino acid (phenylalanine, Phe; or tyrosine, Tyr), F is the venous tracer
infusion rate (μmol·kg-1·min-1) and Ra is the rate of appearance. For calculations of PB,
enrichment (E) is expressed as tracer-to-tracee ratio (TTR); for calculations for PS, mole per
cent excess (MPE; calculated as TTR/(TTR+1)) is used.
Additionally, whole-body kinetics were calculated using modified Steele equations (Steele,
1959; Wolfe & Chinkes, 2005), taking in to account the change in amino acid enrichment and
concentration over time, as follows:
𝑇𝑜𝑡𝑎𝑙 𝑅𝑎(𝑡) = 𝐹− 𝑝𝑉×𝐶(𝑡)×𝑑𝐸(𝑡)
𝐸(𝑡)
(3.8)
𝑇𝑜𝑡𝑎𝑙 𝑅 (𝑡) = 𝑇𝑜𝑡𝑎𝑙 𝑅
− 𝑝𝑉 × 𝑑𝐶(𝑡)
𝑑𝑡
(3.9)
Where for a given amino acid (phenylalanine, Phe; or tyrosine, Tyr), Ra(t) is the rate of
appearance between two consecutive time points; F is intravenous tracer infusion rate

83
(μmol·kg-1·min-1); pV is a constant representing the distribution volume (0.125 L·kg-1); C(t) is
the mean plasma amino acid concentration between 2 consecutive timepoints; dE(t)/dt is the
time-dependent change in plasma amino acid enrichment; E(t) is the mean plasma amino acid
enrichment between 2 consecutive time points as MPE, Rd(t) is the rate of disappearance between
two consecutive time points; and dC(t)/dt is the time-dependent change in plasma amino acid
concentration. Total phenylalanine rate of disappearance (Phe Rd) represents the rate of
phenylalanine hydroxylation and the rate of phenylalanine utilisation for protein synthesis.
Therefore:
𝑃ℎ𝑒 ℎ𝑦𝑑𝑟𝑜𝑥𝑦𝑙𝑎𝑡𝑖𝑜𝑛 = 𝑇𝑜𝑡𝑎𝑙 𝑅
−
𝐸
𝑇𝑦r
(𝑡)
×
𝑇𝑜𝑡𝑎𝑙
𝑅
𝑑
𝑃ℎ𝑒
(3.10)
𝑎
𝑇𝑦𝑟
𝐸
Phe
(𝑡)
𝐹
𝑃ℎ𝑒
+𝑇𝑜𝑡𝑎𝑙
𝑅
𝑑
𝑃ℎ𝑒
𝑃𝑟𝑜𝑡𝑒𝑖𝑛 𝑠𝑦𝑛𝑡ℎ𝑒𝑠𝑖𝑠 (𝑃𝑆) = 𝑇𝑜𝑡𝑎𝑙 𝑅𝑑 𝑃ℎ𝑒 − 𝑃ℎ𝑒 ℎ𝑦𝑑𝑟𝑜𝑥𝑦𝑙𝑎𝑡𝑖𝑜𝑛 (3.11)
Where Ra Tyr is the total rate of tyrosine appearance based on L-[3,3-2H2]-tyrosine infusion and
plasma enrichments, as MPE; and ETyr(t) and EPhe(t) represent the mean plasma L-[ring-2H4]-
tyrosine and L-[ring-2H5]-phenylalanine enrichment between two consecutive time points,
respectively. Total phenylalanine rate of appearance (Phe Ra) represents the rate of appearance
of endogenous phenylalanine (assumed to represent protein breakdown) and exogenous
phenylalanine from the diet. Therefore:
𝑃𝑟𝑜𝑡𝑒𝑖𝑛 𝑏𝑟𝑒𝑎𝑘𝑑𝑜w𝑛 (𝑃𝐵) = 𝑇𝑜𝑡𝑎𝑙 𝑃ℎ𝑒 𝑅𝑎 − 𝐸𝑥𝑜𝑔𝑒𝑛𝑜𝑢𝑠 𝑃ℎ𝑒 𝑅𝑎 − 𝐹𝑃ℎ𝑒 (3.13)
𝑁𝑒𝑡 𝑝𝑟𝑜𝑡𝑒𝑖𝑛 𝑏𝑎𝑙𝑎𝑛𝑐𝑒 = 𝑃𝑆 − 𝑃𝐵 (3.14)

84
For both methods, exogenous phenylalanine rate of appearance over the postprandial period was
calculated by estimating bioavailability (Wolfe et al., 2020), as follows:
𝐸𝑥𝑜𝑔𝑒𝑛𝑜𝑢𝑠 𝑃ℎ𝑒 𝑅𝑎 = 𝑇𝑜𝑡𝑎𝑙 𝑃ℎ𝑒 𝑐𝑜𝑛𝑠𝑢𝑚𝑒𝑑 × 𝑡𝑟𝑢𝑒 𝑖𝑙𝑙𝑒𝑎𝑙 𝑑𝑖𝑔𝑒𝑠𝑡𝑖𝑏𝑖𝑙𝑖𝑡𝑦 −
𝑎𝑏𝑠𝑜𝑟𝑏𝑒𝑑 𝑃ℎ𝑒 ℎ𝑦𝑑𝑟𝑜𝑥𝑦𝑙𝑎𝑡𝑖𝑜𝑛 (3.15)
Where true ileal digestibility was assumed to be 0.96 based on the true ileal digestibility of
phenylalanine from casein (Deglaire & Moughan, 2012) and absorbed phenylalanine
hydroxylation was calculated as the difference in basal to postprandial phenylalanine
hydroxylation rate.
3.3.7
Statistical Analysis
A student’s independent t-test was used to investigate group differences in subject
characteristics. Total incremental area under the curve (iAUC) was calculated for postprandial
amino acid concentrations, with baseline set as the average of basal (-120 – 0 min)
concentrations. Unpaired t-tests were subsequently used to identify differences between
treatments, as well as total AUC for blood glucose, serum insulin and paracetamol
concentrations. All other data were analysed using two-way mixed model ANOVA (time and
treatment factors), with Sidak corrections for multiple comparisons applied when investigating
post hoc differences. Statistical analysis was performed using GraphPad Prism 8 (GraphPad
Software, Inc., San Diego, CA, USA). All data are presented as mean ± SEM, with P < 0.05
indicating statistical significance.

85
3.4
Results
3.4.1
Participant characteristics
No differences in age, height, weight, BMI, or body fat percentage were identified between
groups (Table 3.1; all P > 0.05). Furthermore, habitual diet intake was similar between groups
(P > 0.05).
3.4.2
Glucose, serum insulin and paracetamol concentrations
Blood glucose concentrations (Figure 3.2A) increased from similar basal values following
beverage consumption and were significantly elevated between 15 – 60 min in PLA (P < 0.01
versus 0 min). Conversely, PPB was only elevated at 30 min (P < 0.01 versus 0 min; time x
treatment interaction P < 0.001). Postprandial AUC was 11.6% lower with PPB (P < 0.001).
Serum insulin (Figure 3.2B) was significantly greater than basal between 15 – 60 min in PLA
(P < 0.05), peaking at 30 min (80.0 ± 7.2 mU·L-1). In PPB, the peak at 30 min was significantly
lower (45.4 ± 6.1 mU·L-1; P < 0.05) and significantly greater than insulin concentrations at -
120 min only (time x treatment interaction; P < 0.001). Postprandial AUC following PPB
ingestion was 34.7% lower compared to PLA (P < 0.05).
Serum paracetamol (Figure 3.2C) increased at all timepoint following beverage consumption
(time effect P < 0.001), peaking after 30 min in both groups (24.6 ± 2.3 and 21.8 ± 2.5 mg·L-
1, PLA and PPB, respectively). There was no effect of PPB on serum paracetamol at all
timepoints. Mean AUC, expressed over 1 h and 5 h post-ingestion was similar between groups.
86
Figure 3.2. Arterialised venous A:
glucose; B: insulin; and C:
paracetamol concentrations during a
120 min postabsorptive period and
300 min postprandial period
following protein-polyphenol
ingestion (PPB; n = 10; filled
circles) or an isocaloric
carbohydrate placebo (PLA; n =10;
open circles). Insets represent total
area under the curve for the 300 min
postprandial period. A: Significant
time x treatment interaction effect (P
< 0.001). B: Significant time x
treatment interaction effect (P <
0.001). C: Significant main effects
of time (P < 0.001; post hoc
differences denoted by ***P < 0.001
significantly different to 0 min ).
Treatment differences in AUC and
post hoc differences within time x
treatment interaction effects denoted
by †P < 0.05 significantly different
to PLA at same time point.

87
3.4.3
Plasma amino acid concentrations
Plasma amino acid concentrations are displayed in Figure 3.3. A time x treatment interaction
was observed for all amino acids (P < 0.001). Consumption of PLA did not elevate plasma
amino acid concentrations at any time point relative to 0 min. Between 45 – 300 min, 30 – 120
min and 45 – 240 min, concentrations of phenylalanine (P < 0.05), valine (P < 0.05) and
isoleucine (P < 0.01), respectively, were significantly decreased versus 0 min. At 90 min,
leucine was significantly lower (P < 0.01), whereas tyrosine remained stable. Conversely, PPB
increased plasma concentration of leucine (15 – 90 min; P < 0.05), isoleucine (15 – 120 min;
P < 0.05) and valine (30 – 120 min; P < 0.05) versus 0 min. Additionally, PPB elevated plasma
tyrosine and phenylalanine concentration between 15 – 150 min (P < 0.05) and 30 – 90 min (P
< 0.01) respectively compared to 0 min. During the postprandial period, iAUC of all amino
acids was negative with PLA; conversely, PPB resulted in positive iAUC, which was
significantly greater than PLA (P < 0.001).
=
:
=
£
ss
==
g
2&
g
£223
9%
8
oO
(un
ooe-,.7:10urri)
(,.urw
00€-,
HOw)
‘ONv!
lelpuerdjsog
Nv!
leipueschsog
°
a
So
oO
=
q
2
-=
.
a
£
+
re
°
o
+e
SE
+
SF
sennonecossovoneestcereeey
ie
o
9
So
N
a
géeesea-e
rset:
$s
8
8&8
=&8
$8
888°
=
N
SN
+=
(|-110un)
aursosAy
euseld
(;.710wn)
eursnajos!
ewselg
aa
E
E
£
£
E
E
s
Ss
s
z
=2
ePe4
fe
e@
3223
°8
2
¢
238
sR
2
28
3322
8
2
8
B
(uu
08-,T40UrT!)
(uw
ooc-,
Tour)
(ta
006,
HHount)
‘nv!
reipuesdisog
‘nv
reipuesdisog
NV!
TeIpuEsdssog
a
a
4S
aa
aaa
a
sees
8
eeeeeeg0
S$
®6F
&
2
?:
8§&
688
FB
ak eS
<
(|140un)
eurueje|Aueyd
ewse|g
e
(;.710wm)
auroney
ewselq
‘i
(|-T1owm)
euyea
ewseid
180
240 300
0
30
60
90120
-60
-120
Time
(min)
106

107
Figure 3.3. (Overleaf) Time course of plasma A: phenylalanine; B: tyrosine; C: leucine; D:
isoleucine; E: valine concentrations during a 120 min postabsorptive period and 300 min
postprandial period following protein-polyphenol ingestion (PPB; n = 10; filled circles) or an
isocaloric carbohydrate placebo (PLA; n =10; open circles). Insets represent incremental area
under the curve (iAUC) for the 300 min postprandial period. For all amino acids, significant
time x treatment interaction effects (P < 0.001). Treatment differences in iAUC denoted by
†††P < 0.001 significantly different from PLA. Post hoc differences within time x treatment
interaction effects denoted by †P < 0.05 significantly different to PLA at same time point.
3.4.4
Plasma phenylalanine and tyrosine enrichments
The time course of plasma L-[ring-2H5]-phenylalanine, L-[3,3–2H2]-tyrosine, and L-[ring-2H4]-
tyrosine enrichments are illustrated in Figure 3.4. Infused L-[ring-2H5]-phenylalanine
enrichment was 6.5 ± 0.7 and 6.5 ± 0.8 MPE in PLA and PPB over the basal period (-180 – 0
min). Between 15 – 90 min after beverage consumption, MPE remained stable in PLA but
decreased significantly in PPB (P < 0.05 versus 0 min; time x treatment interaction P < 0.001).
Infused L-[3,3–2H2]-tyrosine enrichments responded similarly, from 3.1 ± 0.4 and 3.2 ± 0.5
MPE in PLA and PPB between -120 – 0 min and remaining stable between 30 – 120 min of
the postprandial period in PLA whilst PPB dropped significantly (P < 0.05 versus 0 min; time
x treatment interaction P < 0.001). Enrichment of hydroxylated L-[ring-2H4]-tyrosine
decreased between 15 – 120 min from 0 min in PPB (P < 0.05) but remained stable across this
time in PLA (time x treatment interaction P < 0.001). Between 120 – 180 min (P < 0.01), at
150 min (P < 0.05), and at 180 min (P < 0.05) in PLA, enrichments of L-[ring-2H5]-
phenylalanine, L-[3,3–2H2]-tyrosine, and L-[ring-2H4]-tyrosine, respectively, were
significantly greater than at 0 min.
108
Figure 3.4. Time course of plasma enrichments (mole per cent excess; MPE) of infused A: L-
[ring-2H5]-phenylalanine and B: L-[3,3–2H2]-tyrosine; and hydroxylated C: L-[ring-2H4]-
tyrosine enrichments, during a 120 min postabsorptive period and 300 min postprandial period
following ingestion of protein-polyphenol intervention (PPB; n = 10; filled circles) or an
isocaloric carbohydrate placebo (PLA; n =10; open circles). Significant time x treatment
interaction effects (P < 0.001) for all enrichments. Post hoc differences within time x treatment
interaction effects denoted by †P < 0.05 significantly different to PLA at same time point.

109
Whole-body protein metabolism
Exogenous phenylalanine Ra was significantly greater with PPB than PLA (67.0 ± 6.6 versus
4.7 ± 1.2 μmol·kg-1·5 h-1; P < 0.001). Over the 5 h postprandial period, 73.1 ± 3.5 % ingested
phenylalanine was calculated to have appeared in circulation. Using equations (3.2) to (3.7) to
calculate whole-body protein kinetics (Figure 3.5A), basal protein breakdown rates exceeded
protein synthesis such that net balance was negative in both PLA and PPB, with no differences
between groups. Protein synthesis and breakdown decreased similarly (by 8.4 ± 0.8% and 11.0
± 1.3%, respectively) during the postprandial period in PLA, resulting in no significant change
in net balance. Whilst breakdown also decreased in PPB with feeding (19.8 ± 4.4%; time effect
P < 0.001), protein synthesis increased 5.0 ± 1.8% (time x treatment interaction P < 0.001) and
was significantly greater than PLA during the postprandial period (P < 0.05). Consequently,
net protein balance became positive with PPB consumption (time x treatment interaction P <
0.001).
Calculated using equations (3.8) to (3.14), whole-body protein kinetics responded to PLA and
PPB feeding in a similar manner (Figure 3.5B). Protein synthesis increased 13.4 ± 2.0% (time
x treatment interaction P < 0.001) with PPB ingestion only and was significantly greater than
PLA during the postprandial period (P < 0.001). Consequently, net balance was positive
following PPB ingestion only (time x treatment interaction P < 0.001).
110
Figure 3.5. Whole-body protein metabolism expressed as area under the curve (μmol
phenylalanine·kg-1·h-1) over a 120 min postabsorptive (basal; solid bars) and 300 min postprandial
period (hashed bars) following ingestion of protein-polyphenol intervention (PPB; n = 10; black
bars) or an isocaloric carbohydrate placebo (PLA; n =10; white bars). Whole-body protein
metabolism calculated using both A: tracer dilution principles and B: Steele equations for non-
steady-state conditions during intravenous L-[ring-2H5]-phenylalanine and L-[3,3-2H2]-
tyrosine infusion. Statistical analyses for synthesis, breakdown, hydroxylation and net balance
performed separately but presented on one graph for presentation purposes. For protein
breakdown, significant main effect for time (P < 0.001; post hoc differences denoted by ***P
< 0.001 significantly different to basal). Post hoc differences within time x treatment effects
(protein synthesis, hydroxylation and net balance) denoted by †P < 0.05, ††P < 0.01, †††P <
0.001 significantly different to PLA at same time point; **P < 0.01, ***P < 0.001 significantly
different to basal within treatment.
111
Figure 3.6. Myofibrillar protein fractional synthesis rate (FSR; expressed as %·h-1) over A:
120 min postabsorptive period (basal), and early (0 – 120 min) and late (120 – 300 min)
postprandial period; and B: 120 min postabsorptive period (basal) and total postprandial period
(0 – 300 min); following ingestion protein-polyphenol (PPB; n = 10; filled circles) or an
isocaloric carbohydrate placebo (PLA; n = 9; open circles). B: significant main effect for time
represented by *P < 0.05 significantly different to basal.

112
3.4.5
Skeletal muscle tracer analyses
One participant in PLA was omitted from the muscle tracer analyses due to insufficient tissue.
Myofibrillar protein-bound L-[ring-2H5]-phenylalanine enrichments were similar between
groups at the start of the basal period (-120 min) and increased over time (time effect P <
0.001), from 0.0030 ± 0.0012 to 0.0054 ± 0.0015 MPE at 0 min in PLA. Enrichment increased
similarly in PPB from 0.0033 ± 0.0005 to 0.0050 ± 0.0007 MPE, -120 to 0 min, respectively.
Between 120 – 300 min into the postprandial period, PLA increased from 0.0102 ± 0.0019 to
0.0153 ± 0.0031 MPE. Myofibrillar protein-bound L-[ring-2H5]-phenylalanine enrichments
increased with PPB to a similar extent, from 0.0078 ± 0.0008 to 0.0128 ± 0.0010 MPE from
120 to 300 min, respectively, with no difference between groups.
Myofibrillar FSR (Figure 3.6) was calculated using the AUC for plasma L-[ring-2H5]-
phenylalanine enrichment over time. Mean myoFSR increased from the basal to postprandial
period by 0.013 ± 0.005 and 0.023 ± 0.005 %·h-1 in PLA and PPB respectively (time effect P
< 0.05). However, there was no effect of PPB on myofibrillar FSR compared to PLA. Separated
into early (0 – 120 min) and late (120 – 300 min) postprandial phases (Figure 3.6B), mean
myoFSR across groups was 0.016 ± 0.003 (basal), 0.032 ± 0.006 (early) and 0.025 ± 0.004
%·h-1 (late). However, no significant effects were observed.
3.5
Discussion
This study aimed to investigate the anabolic response following consumption of a mixed
protein and polyphenol blend that was targeted at increasing and sustaining amino acid
availability. We focussed on early and late postprandial rates of myofibrillar protein synthesis
and characterised whole-body protein turnover versus isocaloric carbohydrate placebo to
determine the influence of exogenous amino acid availability per se. As hypothesised,

113
intervention with a mixed protein-polyphenol beverage induced pronounced plasma
aminoacidaemia and resulted in a change to positive net protein balance. Rates of myofibrillar
protein synthesis increased by ~69% from basal during the postprandial period. However, this
rise was observed in both protein and placebo treatments, demonstrating a clear disconnect
between whole body and skeletal muscle protein synthesis and suggesting that mechanisms
other than those pertaining to exogenous amino acids may contribute to MyoPS stimulation.
In the absence of other macronutrients, the post-prandial elevation in muscle protein synthesis
rates is driven by the rise in plasma essential amino acid concentration (Churchward-Venne et
al., 2012; Tipton et al., 1999; Volpi, Kobayashi, Sheffield-Moore, Mittendorfer, & Wolfe,
2003). Of these, the magnitude of leucinaemia in particular correlates closely with muscle
protein synthesis rates (Pennings et al., 2011a). Data obtained in vitro indicate that leucine
enhances phosphorylation of mTORSer2448 and of the downstream effectors 4EBP1Thr37/46,
p70S6KThr389 and rps6Ser235/236 (Atherton et al., 2010b) and promotes mTOR translocation to
the lysosome (Sancak et al., 2010). In the present study, consumption of 20 g protein in the
PPB intervention increased plasma concentrations of essential amino acids, including leucine,
preventing the decline that was otherwise observed in PLA. This rise was maintained over the
early (0 – 120 min) postprandial period and was significantly greater than PLA at the start of
the later period of investigation. Accordingly, we observed two-fold greater rates of MyoPS
throughout the 5 h postprandial period in the PPB group, in agreement with previous work
(Reitelseder et al., 2019; van Vliet et al., 2019). Furthermore, although rates of whole-body
phenylalanine appearance from breakdown decreased ~15% in both groups, disappearance to
synthesis was ~14% greater with PPB creating positive net protein balance (Figure 3.5) as
demonstrated previously (Koopman et al., 2006; Koopman et al., 2005; Miller et al., 2003),
creating an anabolic milieu attributable to exogenous amino acids. Thus, this nutritional
strategy may be applicable to models of recovery and hypertrophy (as will be explored in

114
Chapters 4 and 5) where amino acid demand is greater (Biolo et al., 1997; West, Abou Sawan,
Mazzulla, Williamson, & Moore, 2017).
Ingesting a mixed-protein blend has been demonstrated to increase both early and late rates of
MyoPS (van Vliet et al., 2019). Specifically, consumption of 38 g milk protein concentrate
(containing both whey and casein proteins) maintains high plasma phenylalanine and leucine
concentrations for 300 min and stimulates both early (0 – 120 min) and late (120 – 300 min)
rates of MyoPS by ~72% and ~80% respectively compared to basal (van Vliet et al., 2019).
This may be mediated in part by greater amino acid availability to the muscle, as complete
protein sources maintain rates of MyoPS versus consumption of isolated amino acids and
amino acid-metabolites only (Churchward-Venne et al., 2014; Churchward-Venne et al., 2012;
Fuchs et al., 2019). In the present study, we used a mixed-protein blend targeted at maintaining
aminoacidaemia throughout the postprandial period (i.e., beyond 120 min) to determine
whether this supported greater rates of MyoPS compared to placebo. Whilst PPB increased
amino acid concentrations relative to PLA at the start of the later phase, this rise did not persist
throughout the postprandial period. Furthermore, we were unable to identify greater temporal
resolution in the MyoPS response during this time. Specifically, our results show that MyoPS
was not significantly elevated with feeding at any sub-timepoint (Figure 3.6A). This finding
contrasts with our observation over the cumulative postprandial period and research by others
(Churchward-Venne et al., 2014; Fuchs et al., 2019; van Vliet et al., 2019). Indeed, this
observation (or lack thereof) likely relates to the heterogeneity of the response between
participants, and the increased sensitivity required when analysing successive muscle biopsy
samples over relatively short periods of time. Consequently, we cannot delineate the
relationship with prolonged plasma amino acid concentration to determine whether MyoPS is
prolonged by substrate availability.

115
Part of the impetus of the current study was to include an isocaloric, but non-nitrogenous
placebo comparison group to determine the effects of the protein-polyphenol intervention and
exogenous amino acid availability per se on protein turnover and, in particular, MyoPS. In the
present study, PLA suppressed rate of appearance from whole-body protein breakdown, as
expected (Borsheim et al., 2004b; Gelfand & Barrett, 1987; Moller-Loswick et al., 1994;
Tessari et al., 1986). The gradual increase in plasma enrichment between 120 – 180 min
following PLA consumption is reflective of reduced amino acid release into plasma (Figure
3.3), suggesting suppressed whole body breakdown (Figure 3.5), possibly mediated by insulin
in healthy individuals (Biolo et al., 1995a; Borsheim et al., 2004b; Fukagawa et al., 1986;
Gelfand & Barrett, 1987; Koopman et al., 2006; Tessari et al., 1986). The importance of an
isocaloric placebo was highlighted as an important area for investigation based off recent work
indicating that even suboptimal doses of protein or amino acids initially stimulate MyoPS to a
similar degree as larger, more optimal protein boluses (Churchward-Venne et al., 2014;
Churchward-Venne et al., 2012). However, such studies typically compare the postprandial
response to differing protein and/or amino acid compositions (Burd et al., 2015; Churchward-
Venne et al., 2014; Churchward-Venne et al., 2012; Churchward-Venne et al., 2019a, 2019b;
Fuchs et al., 2019; Reidy et al., 2014; Reitelseder et al., 2011; Wilkinson et al., 2013), making
it difficult to determine whether exogenous amino acid provision is a prerequisite to MyoPS
stimulation. Whilst a reduction in circulating amino acids may serve to suppress or prevent an
increase in muscle protein synthesis rates (Bohe et al., 2003; Tessari et al., 1986), interestingly,
in the present study MyoPS increased ~46% with PLA and was not significantly different to
PPB.
The suggestion that exogenous amino acids are not necessary for stimulating MyoPS at rest
may appear counterintuitive, and potentially the result of an experimental phenomenon in the
present study. Importantly, we cannot isolate the effects of feeding alone from other,

116
extraneous variables, including any influence of our testing protocol and/or circadian rhythm
on protein metabolism (Dyar et al., 2018; Zimmet, Wall, Rome, Stimmler, & Jarrett, 1974).
Indeed, paracetamol suppresses rates of mixed muscle protein synthesis after damaging
exercise, albeit this may be through constitutive inhibition of post-exercise prostaglandin
synthesis (Trappe, Fluckey, White, Lambert, & Evans, 2001; Trappe et al., 2002) rather than
through acute, direct activity (Mikkelsen et al., 2011). However, the stimulation of MyoPS
with both carbohydrate and protein feeding is intriguing and requires further attention. The
observations that fast-digesting proteins and intravenous amino acid infusions cause a
refractory MyoPS response after 90 – 120 min despite elevated amino acid availability
(Atherton et al., 2010a; Bohe et al., 2001) are difficult to reconcile against other instances
whereas repeated protein feedings (Mitchell et al., 2015) or blends of fast and slow-digesting
proteins (Holm et al., 2010; van Vliet et al., 2019) result in prolonged aminoacidaemia and
sustained stimulation of MyoPS between 120 – 300 min following consumption. However,
these findings together with those in the present study would be consistent with feeding-related
mechanism contributing to the stimulation of MyoPS, perhaps mediated via previously
unidentified energy-sensing factors within the gastrointestinal tract or splanchnic bed. That is,
the refractory nature of MyoPS observed with fast-digesting proteins and amino acid infusion
may be caused by an absence of nutrients being digested and absorbed. Age-related differences
in protein metabolism notwithstanding, infusion of glucagon-like peptide (GLP-1) has been
demonstrated to increase MyoPS ~62% in individuals aged 65 – 75 years old (Abdulla et al.,
2020), supporting a role for incretin hormones in mediating muscle metabolism. Nonetheless,
if carbohydrate was capable of stimulating MyoPS, the origin of a substrate in the absence of
exogenous protein is unclear, given that circulating amino acid concentrations fell. Indeed,
carbohydrate feeding has been observed to reduce muscle protein breakdown, as reflected by
the release of phenylalanine from the muscle into the vein (Borsheim et al., 2004b), and insulin

117
per se is not considered to promote muscle protein synthesis due to the lowering of systemic
amino acid concentrations (Trommelen, Groen, Hamer, de Groot, & van Loon, 2015).
However, whilst the current data cannot answer this question, an alternative explanation is that
proportionally more phenylalanine from breakdown is resynthesised into muscle protein than
is released. Indeed, accounting for the kinetics of the intramuscular amino acid pool, muscle
protein breakdown remains constant upon the infusion of insulin, whereas release into
circulation decreases as proportionally more amino acids are resynthesised into muscle protein
(Biolo et al., 1995a). Thus, amino acids from the breakdown of intracellular protein may
provide a substrate for myofibrillar protein synthesis in the present study. Further research on
net protein balance is warranted, as it is unclear whether exogenous protein provision prevented
intracellular breakdown given the increase in whole-body protein synthesis (i.e., rate of plasma
disappearance).
Despite a possible mechanistic basis, existing literature tends not to support the stimulation of
muscle protein synthesis with carbohydrate (Borsheim et al., 2004b; Koopman et al., 2006;
Koopman et al., 2005; Tang et al., 2007). However, in the present study, tracer incorporation
was analysed in the myofibrillar protein subfraction. The assumption that exogenous protein-
derived amino acids and not carbohydrate would influence MyoPS was based on existing
literature that considers intramuscular amino acids and protein as a single pool (Borsheim et
al., 2004b; Koopman et al., 2006; Koopman et al., 2005; Tang et al., 2007). Nonetheless,
regulation of turnover in myofibrillar and mixed-muscle protein pools may differ; for example,
rates of mixed-muscle but not myofibrillar protein breakdown appear influenced by
hyperinsulinaemia (Moller-Loswick et al., 1994), although this may also represent a
repartitioning of amino acids toward protein synthesis as previously discussed. Furthermore,
protein (Koopman et al., 2006; Miller et al., 2003), but not carbohydrate (Borsheim et al.,
2004b) stimulates mixed muscle protein synthesis, but equal stimulation of the myofibrillar

118
subfraction has been observed between whey, casein and carbohydrate feeding in older males
(Agergaard et al., 2017; Reitelseder et al., 2019). Whilst age-related differences in protein
absorption and metabolism (Katsanos et al., 2005; Volpi et al., 1999; Wall et al., 2015) may
have impaired the protein synthetic response in the aforementioned studies, notably, these
appear to be the only investigations to date on the influence of carbohydrate on MyoPS at rest
and is in agreement with the present findings. In the remaining literature, additional factors
such as resistance exercise, absence of a postabsorptive period, and the use of positive controls,
make the effects of exogenous amino acid provision difficult to isolate from feeding alone.
However, such works have not detected differences in fed state MyoPS following the ingestion
of different experimental beverages or meals intended to manipulate amino acid availability
(Burd et al., 2015; Churchward-Venne et al., 2014; Churchward-Venne et al., 2012;
Churchward-Venne et al., 2019a, 2019b; Davies et al., 2020; Fuchs et al., 2019; Gorissen et
al., 2017; Rahbek et al., 2014; Reidy et al., 2014; Reitelseder et al., 2011; Wilkinson et al.,
2013). Certainly, together with the present data, these studies support the suggestion that
additional factors rather than exogenous amino acid availability per se may underpin the acute
myofibrillar protein synthetic response. Whether these are related to energy provision and
gastrointestinal and/or intramuscular factors is an important area for future research.
The use of intrinsically labelled proteins allows for the rate of exogenous amino acid
appearance to be calculated directly, by measuring plasma enrichment of the ingested label
(Boirie et al., 1996; van Loon et al., 2009; van Vliet et al., 2019). As such, data from 18
randomised controlled trials indicates that approximately 50% of dietary-protein-derived,
intrinsically-labelled phenylalanine appears in the circulation over a 5 h postprandial period
(Gorissen et al., 2020). However, this approach has been suggested to lead to an
underestimation of the true rate of appearance due to dilution of the tracer in the gastrointestinal
tract and splanchnic bed (Wolfe et al., 2020; Wolfe et al., 2019). For example, simultaneous

119
digestion of other endogenous proteins in the gastrointestinal tract will contribute unlabelled
phenylalanine before appearing in splanchnic circulation, and splanchnic protein turnover will
remove labelled tracer even in the absence of a net change in splanchnic protein synthesis. In
the present study, we used an alternative bioavailability approach based on the true ileal
digestibility of phenylalanine and calculating loss to hydroxylation with feeding (Equation
3.15) (Wolfe et al., 2020; Wolfe et al., 2019). Although we did not experimentally verify true
ileal digestibility, previous work has shown this to be highly conserved across in humans after
consumption of both intact and hydrolysed milk proteins, at 96% (Deglaire & Moughan, 2012).
Interestingly, this approach as applied to the present data indicated that ~73% of ingested
phenylalanine appeared in circulation over this time. Although we did not conduct an internal
comparison between methods, our calculations of whole-body protein turnover agree
qualitatively with previous work using intrinsically-labelled proteins (Boirie et al., 1996;
Pennings et al., 2012; van Vliet et al., 2019). This suggests that the bioavailability approach
may be an appropriate alternative for when intrinsically labelled proteins are not available.
However, we cannot determine the accuracy of either approach based on the current work, and
the apparent discrepancies (i.e., ~50% reported previously versus ~73% at present) highlight
important considerations in study design when assessing postprandial protein handling.
In conclusion, this study provides novel insight into the relationship between amino acid
availability and the upregulation of myofibrillar protein synthesis. Ingestion of a mixed-protein
and polyphenol beverage increased plasma amino acid concentrations and increased whole-
body net protein balance versus a carbohydrate placebo, suggesting this nutritional approach is
applicable to situations where amino acid availability may limit whole body and muscle protein
metabolism. Contrary to our hypothesis, both protein and placebo treatments stimulated rates
of myofibrillar protein synthesis by ~69% indicating that exogenous amino acid availability
per se does not determine the myofibrillar protein synthetic response at rest. Future work is

ed
120
required to delineate this relationship and increase the temporal resolution on myofibrillar
protein synthesis and amino acid availability.

121
Chapter 4 - Improved Recovery From Skeletal Muscle Damage is Largely
Unexplained by Myofibrillar Protein Synthesis or Inflammatory and
Regenerative Gene Expression Pathways
The work contained in this chapter is published:
Pavis, G. F., Jameson, T. S. O., Dirks, M. L., Lee, B. P., Abdelrahman, D. R., Murton, A. J., .
. . Stephens, F. B. (2020). Improved recovery from skeletal muscle damage is largely
unexplained by myofibrillar protein synthesis or inflammatory and regenerative gene
expression pathways. American Journal of Physiology: Endocrinology and Metabolism.
doi:10.1152/ajpendo.00454.2020

122
4.1
Abstract
The contribution of myofibrillar protein synthesis (MyoPS) to recovery from skeletal muscle
damage in humans is unknown. Recreationally active males and females consumed a daily
protein-polyphenol beverage targeted at increasing amino acid availability and reducing
inflammation (PPB; n = 9), both known to affect MyoPS, or an isocaloric placebo (PLA; n =
9) during 168 h of recovery from 300 maximal unilateral eccentric contractions. Muscle
function was assessed daily. Muscle biopsies were collected 24, 27, 36, 72 and 168 h for
MyoPS measurements using 2H2O and expression of 224 genes using RT-qPCR and pathway
analysis. PPB improved recovery of muscle function, which was impaired for five days
following eccentric exercise in PLA (interaction; P < 0.05). Acute postprandial MyoPS rates
were unaffected by nutritional intervention (24 – 27 h). Prior eccentric exercise increased
overnight (27 – 36 h) MyoPS versus control leg (PLA: 33 ± 19%; PPB: 79 ± 25%; leg P <
0.01), and PPB tended to increase this further (interaction P = 0.06). Daily MyoPS rates were
greater with PPB between 72 – 168 h after eccentric exercise, albeit after function had
recovered. Inflammatory and regenerative signalling pathways were dramatically upregulated
and clustered following eccentric exercise but were unaffected by nutritional intervention.
These results suggest that accelerated recovery from eccentric exercise is not explained by
elevated MyoPS or suppression of inflammation.

123
4.2
Introduction
The ability of skeletal muscle to regenerate and recover following damage is crucial for
regulating muscle mass, muscle function and disease resistance (Keys et al., 1950; Mitchell et
al., 2012; Relaix & Zammit, 2012). In mice, the recovery of contractile function 48 – 120 h
following exercise-induced muscle damage is associated with increased rates of mixed muscle
protein synthesis and breakdown (Lowe et al., 1995). Whilst a degree of inflammation appears
necessary for this recovery process (Hyldahl et al., 2011; Lowe et al., 1995; Saclier et al., 2013),
aberrant inflammation suppresses rates of muscle protein synthesis (Lang, Frost, & Vary, 2007)
and may delay regeneration and recovery following muscle damage (Mackey et al., 2016;
Raimondo & Mooney, 2018). Indeed, polyphenols with known anti-inflammatory properties
attenuate post-exercise inflammatory signalling in mice (Davis et al., 2007) and accelerate
functional recovery following muscle damage in humans (Trombold et al., 2010). Given that
muscle damage is characterised by a loss in contractile function and damage to contractile
proteins (Warren et al., 1999), satellite cells and pericytes associate with damaged myofibers,
and that small heat shock proteins aggregate with myofibrils during recovery (Dellavalle et al.,
2011; Mackey et al., 2016; Paulsen et al., 2007; Saclier et al., 2013), the synthesis of
myofibrillar proteins (MyoPS) in particular may be critical to the recovery process. However,
the time course and therefore relative importance of MyoPS during recovery, particularly in
humans, is unknown due to a lack of intervention studies that utilise direct measures.
Eccentric muscle contractions safely and effectively induce transient skeletal muscle damage
in humans. Maximal contractile force, considered the most reliable indirect measure of muscle
damage (Warren et al., 1999), is reduced 15 – 30% 24 h after eccentric exercise, persisting for
several days depending on the intensity of eccentric exercise (Farup et al., 2014a; Vissing et
al., 2008). Eccentric, rather than concentric, contractions induce greater myofibrillar disruption
(Moore et al., 2005) and coincide with elevated rates of mixed muscle (Phillips et al., 1997)

124
and myofibrillar protein synthesis (Moore et al., 2005). Protein ingestion increases rates of
muscle protein synthesis and signalling through the mammalian target of rapamycin (mTOR)
pathway over and above the effect of exercise alone (Biolo et al., 1997; Moore, Atherton,
Rennie, Tarnopolsky, & Phillips, 2011). In mouse models, pharmaceutical inhibition of mTOR
complex 1 delays recovery of muscle function by 20% at 7 days after eccentric contraction-
induced muscle damage (Baumann, Rogers, Otis, & Ingalls, 2016). In humans, protein
ingestion has been shown to accelerate recovery of function, including measures of both peak
torque and work done, following resistance exercise (Davies et al., 2018). However, to date
very limited mechanistic insight exists to explain these positive findings.
Traditional stable isotope tracer methodologies allow for MyoPS rates to be quantified over
the duration of an intravenous infusion, which is typically limited to several hours. Therefore,
this approach is not suitable for a comprehensive measurement of MyoPS over the full duration
of recovery from eccentric exercise. An alternative method involving deuterium oxide (2H2O)
consumption allows for MyoPS rates to be determined in “free-living” conditions outside of a
laboratory setting, due to the endogenous synthesis of deuterium-labelled alanine (Dufner et
al., 2005; Scalzo et al., 2014; Wilkinson et al., 2015; Wilkinson et al., 2014). If the body water
pool remains appropriately enriched, the 2H2O method allows for the simultaneous
characterisation of daily, cumulative protein synthesis rates to capture the full recovery process,
as well as shorter, hourly rates to further the understanding of MyoPS across certain
physiological states, such as post-prandial or overnight conditions that may be influenced by
immediate amino acid availability. Capturing these time periods in tandem allows for the
determination of whether temporal alterations in MyoPS rates coincide with skeletal muscle
recovery and are therefore consistent with being a primary mechanism dictating muscle
recovery.

125
We hypothesised that amino acid availability and excessive inflammation would limit MyoPS
following muscle damage, such that nutritionally targeting these processes with a post-exercise
protein and polyphenol nutritional intervention would suppress inflammation and increase
MyoPS and associated signalling, resulting in improved muscle recovery. To this end, we
sought to maximise rates of MyoPS with the addition of concentric exercise during the recovery
period. We aimed to characterise the time course of rates of MyoPS and key gene expression
pathways of inflammation, protein synthesis, proteolysis and substrate metabolism over a week
of recovery following voluntary eccentric muscle contractions in humans for the first time,
whilst fully controlling diet and resistance exercise.
4.3
Methods
4.3.1
Participants
An a priori power calculation was performed using the expected effect size (0.64) of whey
protein over placebo ingestion on isokinetic muscle function 24 h after maximal eccentric
exercise, based on previous work (Cooke et al., 2010). Assuming 80% power and α = 0.05, we
aimed to recruit 9 participants per group. Accordingly, 18 healthy, recreationally active,
participants were recruited (11 male, 7 female; age: 22 ± 1 y; body mass: 75.2 ± 2.7 kg; body
mass index (BMI): 24.3 ± 0.8 kg·m-2). Recreationally active was defined as participating in
sporting activities > 2 h per week but not following a structured exercise training program.
Exclusion criteria were: (1) diagnosed metabolic or cardiovascular impairment; (2) self-
reported habitual protein intake < 0.8 g·kg-1·d-1; (3) musculoskeletal injury that may impair
exercise performance; and/or (4) engagement in systematic resistance training within six
months of participation.

126
All individuals provided written consent at least 24 h following verbal and written explanation
of the experimental procedures, which were approved by the University of Exeter’s Sport and
Health Sciences Research Ethics Committee (Ref. No. 161026/B/06). This study was registered
as a clinical trial with ClinicalTrials.gov (NCT02980900).
Table 4.1. Subject characteristics and details of the controlled diet
PLA
PPB
(n = 9)
(n = 9)
Sex (male:female)
6:3
5:4
Age (y)
22 ± 0
22 ± 1
Body mass (kg)
77.6 ± 4.1
72.8 ± 3.6
Height (cm)
176.2 ± 1.2
175.5 ± 2.0
BMI (kg·m-2)
25.0 ± 1.4
23.6 ± 0.9
Baseline function (CON leg; J)
2824 ± 165
2593 ± 140
Baseline function (ECC leg; J)
2932 ± 130
2527 ± 163
Energy (MJ·day-1)
12.1 ± 0.3
11.9 ± 0.5
Protein (g·kg-1·day-1)
1.2 ± 0.0
1.5 ± 0.0***
Protein (g·day-1)
93 ± 4
108 ± 5*
Carbohydrate (g·day-1)
394 ± 12
372 ± 14
Fat (g·day-1)
98.5 ± 3.5
94.4 ± 5.4
Values represent mean ± SEM. PLA, maltodextrin placebo condition; PPB, protein-polyphenol
supplement; BMI, body mass index; CON, concentric-only leg; ECC, eccentric + concentric
leg; *P < 0.05, ***P < 0.001 significantly different to PLA.

127
4.3.2
General Study Design
Participants were randomly assigned in a double-blind, placebo-controlled, parallel-group
design, counter-balanced for leg dominance, to consume either a daily post-exercise protein-
polyphenol beverage (PPB; n = 9) or iso-caloric carbohydrate placebo (PLA; n = 9). Participant
characteristics are shown in Table 4.1.
A schematic overview of the study protocol is presented in Figure 4.1. Following enrolment,
participants visited the laboratory at least 48 h before the start of the study for anthropometric
measures and familiarisation to the testing procedures. Individual settings for the isokinetic
dynamometer (Biodex System 3, Biodex Medical Systems, Inc., Shirley, NY, USA) were
determined on this visit and used for all subsequent visits. Full dietary control was employed
from the baseline visit (-144 h) to 168 h post-eccentric exercise (14 days total). The
experimental beverages (see 4.3.5 Diet and nutritional intervention) were consumed once
daily, either immediately post-exercise during laboratory visits to increase amino acid
availability, or at 2000 h on the days prior to eccentric exercise, as similar durations of
polyphenol dosing reportedly accelerate recovery from eccentric exercise (Trombold et al.,
2010). Participants were instructed to abstain from strenuous physical activity, alcohol and
anti-inflammatory or analgesic medication 48 h prior to and throughout the experimental
protocol. Caffeine ingestion was recorded and only permitted > 6 h before a study visit.
Maximal isokinetic voluntary contraction (muscle function) and soreness of the knee extensor
muscles were assessed 144 h prior to eccentric exercise (baseline; see 4.3.4 Muscle soreness
and maximal isokinetic function). At ~1900 h on the day of eccentric exercise (t = 0 h),
participants carried out 300 maximal unilateral eccentric contractions of the knee extensors
designed to elicit muscle damage. Follow up tests of muscle function and muscle soreness were
made every 24 h following the eccentric protocol for 168 h. All lab visits, with the exception
128
of a fasted visit at 36 h, took place 1.5 h after consuming the final meal of the day. Bilateral
muscle biopsy samples were collected from the eccentrically exercised leg (ECC) and the
rested control leg (CON) before completing the functional assessment at 24, 72 and 168 h.
Figure 4.1. Graphical representation of the experimental protocol. ECC, eccentric leg only;
C+E, control + eccentric legs. Oral consumption of 70% 2H2O began at ~0800 h on the day of
eccentric exercise with 8 x 6 mL·kg-1 doses consumed every 1.5 h and maintained thereafter
with daily doses of 0.54 mL·kg-1. Unilateral eccentric exercise performed at ~1900 h (t = 0 h)
with follow up tests of muscle function and soreness performed every 24 h thereafter. Bilateral
muscle biopsies obtained at 24, 27, 36, 72 and 168 h after eccentric exercise. Blood sampling
performed daily prior to the function test, as well as prior to muscle biopsies at 27 and 36 h.
Full dietary control providing 1.2 g·kg-1·d-1 dietary protein was employed throughout the study,
in addition to daily consumption of a protein-polyphenol beverage or isocaloric maltodextrin
placebo.

129
To investigate the effect of nutritional intervention on postprandial muscle metabolism,
participants rested in a semi-supine position for 3 h following the consumption of the
experimental beverage at 24 h, after which time additional bilateral biopsies were taken
(corresponding to 27 h post-eccentric exercise). All participants were given a maltodextrin
beverage before leaving the laboratory and were asked to return the following morning (36 h
post-eccentric exercise) for further bilateral muscle biopsies in order to investigate the effect
of post-exercise nutritional intervention on overnight recovery. Venous blood samples were
collected from the antecubital vein via venepuncture technique into lithium heparin containers
upon arrival to the laboratory at baseline and daily between 24 and 168 h. Additional blood
samples were collected before the muscle biopsies at 27 and 36 h. Samples were immediately
centrifuged at 2850 x g for 10 min at 4°C and plasma was aliquoted, snap-frozen in liquid
nitrogen and stored at -80°C for further analysis.
4.3.3
Eccentric contraction protocol
One leg was randomly assigned to undergo the unilateral damaging exercise protocol, which
consisted of 10 sets x 30 repetitions of maximal isokinetic eccentric contractions of the knee
extensors. An isokinetic dynamometer was used with an angular velocity of 60 deg·s-1. Each
set was separated by 120 s rest. Knee joint range of motion was determined as 80° from full
flexion, as muscle damage is more prevalent at longer muscle lengths (Newham, Jones, Ghosh,
& Aurora, 1988). Participants received visual and verbal feedback and encouragement to
ensure maximal effort throughout each repetition.
4.3.4
Muscle soreness and maximal isokinetic function

130
Upon arrival to the laboratory, participants were asked to rise from a seated position and rate
general muscle soreness on a 100 mm visual analogue scale (VAS) going from “no pain at all”
(0 mm) to “worst possible pain” (100 mm), as described previously (Bijur et al., 2001).
Bilateral assessment of maximal voluntary isokinetic muscle function was performed with one
set of 30 maximal isokinetic concentric contractions of the knee extensors through 80° range
of motion equidistant from full flexion and full extension. Angular velocity was 75 deg·s-1. A
further four sets of 30 repetitions were carried out in the ECC leg after the functional
assessment to provide an exercise stimulus. In the CON leg, further sets of 30 repetitions were
performed at 24 h until total work was matched between legs in order to standardise the effects
of exercise on postprandial and overnight recovery. Otherwise between 48 – 168 h, four
additional sets were completed after the functional assessments. Each set of 30 repetitions was
separated by 60 s rest.
Isokinetic muscle function was calculated as the area under the torque-time graph (J), which
was sampled using an analogue-to-digital converter (Power1401-3A, Cambridge Electronic
Design Ltd., Cambridge, UK) and recorded using Spike2 software (Cambridge Electronic
Design Ltd) for off-line analysis. Data were expressed relative to the control leg (%CON) to
correct for any influence of the testing procedures on contractility of the muscle.
4.3.5
Diet and nutritional intervention
Due to the hypothesis that amino acid availability would limit recovery, it was imperative that
diet was strictly controlled. As such, the controlled diet was designed to maintain energy
balance and provide 1.2 g·kg body mass-1·d-1 protein (Table 4.1), which is within ACSM
guidelines to support metabolic adaptation (Thomas et al., 2016) but importantly, below current
recommendations to maximise muscle protein anabolism (Morton et al., 2018). All food was

131
weighed out, individually packaged and provided in a container corresponding to the day of
the week. Energy requirements were based on the Henry equation (Henry, 2005) multiplied by
an activity factor of 1.6. Body mass was recorded on each laboratory visit to allow adjustments
to the diet if necessary. Participants were informed of the importance of diet adherence and
returned forms indicating whether each item was consumed. No other foods or energy-
containing beverages were permitted throughout the study.
The nutritional intervention provided in PPB was a commercially available post-exercise
beverage (Beachbody Performance Recover, Beachbody LLC, Santa Monica, CA, USA)
containing 20 g total protein (from a blend of whey, pea and casein), 10 g total carbohydrate
and 650 mg pomegranate extract (211 mg polyphenols; full composition shown in Appendix
2). Participants in the PLA group received an isocaloric maltodextrin placebo. Both groups
were given a maltodextrin drink containing 24 g carbohydrate to consume each night
approximately 30 min before sleep.
4.3.6
Deuterated water dosing protocol
The full details of the deuterated water dosing protocol are presented in Chapter 2. Briefly, the
protocol was designed to enrich the body water pool to 0.6% and consisted of one loading day
followed by seven maintenance days. This was adapted from previous work from our
laboratory (Kilroe et al., 2020) as total body water (i.e. the precursor pool) is largely influenced
by body mass (Watson et al., 1980) and previous loading protocols have not achieved a true
steady-state of precursor pool enrichment (Kilroe et al., 2020; Wilkinson et al., 2014). Thus,
the present protocol was based on the assumption that the body water pool contributes 60 -
70% body mass in healthy lean individuals (Watson et al., 1980) and turns over at 7 – 10 %·d-
1 (Shimamoto & Komiya, 2000). The loading protocol commenced at ~0800 h on the day of

132
eccentric exercise (t = -11 h) with the consumption of 6 mL·kg-1 70% 2H2O (Cambridge
Isotopes Laboratories, Andover, MA, USA), separated into eight equal doses to be consumed
every 1.5 h (i.e., 8 x 0.75 mL·kg-1). Participants remained in the laboratory until four doses had
been consumed to ensure no vertigo or dizziness occurred, before leaving the laboratory with
the remaining four doses. Body water enrichment was maintained thereafter with one daily
dose of 0.54 mL·kg-1 consumed upon waking.
4.3.7
Muscle biopsy collection
Muscle biopsies were obtained under local anaesthesia (2% lidocaine) from the mid-section of
the m. vastus lateralis by the Bergström needle technique modified for suction (Tarnopolsky
et al., 2011). All samples were rapidly dissected of visible fat and connective tissue, frozen in
liquid-nitrogen-cooled isopentane and stored at -80°C until subsequent analysis.
4.3.8
Plasma analyses
Plasma samples were analysed for creatine kinase (CK) by photometric activity assay using
Cobas 8000 automated analyser (Roche Diagnostics, Indianapolis, IN, USA). Hydrogen
isotope ratios (2H/1H ) of plasma were determined in triplicate by injecting samples into a high-
temperature conversion elemental analyser (TCEA Flash 2000, ThermoFisher Scientific,
Waltham, MA, USA) coupled to an isotope ratio mass spectrometer (IRMS; Delta V,
ThermoFisher Scientific). Raw isotope ratio values were normalised with in house reference
materials calibrated to Vienna Standard Mean Ocean Water (VSMOW).
4.3.9
Myofibrillar bound [2H]-alanine enrichment

133
Myofibrillar protein fractions were isolated from ~50 mg wet weight muscle tissue as described
in Chapter 2. Tissue was homogenised in 7.5 μL· mg-1 ice-cold homogenisation buffer (50 mM
Tris·HCl pH 7.4, 1 mM EDTA, 1 mM EGTA, 10 mM β-glycerophosphate salt, 50 mM NaF
and 0.5 mM activated Na3VO4; Sigma-Aldrich Company Ltd., Dorset, UK) with a complete
protease inhibitor cocktail tablet (1 tablet per 50 mL of buffer; Roche, West Sussex, UK) using
a glass pestle. Homogenates were centrifuged at 2200 x g for 10 min at 4°C and the supernatant
representing the sarcoplasmic pool was aliquoted and stored at -80°C for subsequent western
blot analysis. The remaining pellet was washed with 500 μL homogenisation buffer followed
by centrifugation at 700 x g for 10 min at 4°C. Myofibrillar proteins were solubilised in 0.3 M
NaOH for 30 min at 50°C and separated from the insoluble collagen fraction by centrifugation
at 10,000 x g for 5 min at 4°C. The remaining supernatant was aliquoted and myofibrillar
proteins were precipitated with 1 M perchloric acid and centrifuged at 700 x g for 10 min at
4°C. The myofibrillar pellet was washed twice in 1 mL 70% ethanol and hydrolysed in 2 mL
6 M HCl at 110°C for 24 h. The samples were subsequently dried under a vacuum (SavantTM
SpeedVacTM, ThermoFisher Scientific) and reconstituted in 3 mL 25% acetic acid. Samples
were passed over cation exchange resin columns (100 – 200 mesh; H+ form; Dowex 50WX8;
Sigma-Aldrich Company Ltd.) and eluted with 6 M NH4OH, before being dried under vacuum.
Samples were resuspended in 1 mL distilled water and 1 mL 0.1% formic acid in acetonitrile
and spun at 10,000 x g for 3 min at 4°C. The supernatant was aliquoted, dried under a vacuum
and stored at -20°C.
Following derivatisation of the purified amino acids to tert-butyl-dimethylsilyl (TBDMS)
esters (Molnár-Perl & Katona, 2000), 1 μL of the sample was injected into a Delta V Advantage
IRMS (ThermoFisher Scientific) fitted with a Trace 1310 gas chromatograph. The peaks were
resolved on a 30m × 0.25mm ID × 0.25μm film DB-5 capillary column (Agilent Technologies,
Santa Clara, CA, USA; temperature program: 110°C for 1 min; 10°C∙min-1 ramp to 180°C;

134
5°C∙min-1 ramp to 220°C; 20°C∙min-1 ramp to 300°C; hold for 2 min) prior to pyrolysis. Amino
acids eluting from the gas chromatograph were combusted through use of an in-line pyrolysis
reactor to thermally decompose the amino acids to their elemental components prior to entry
into the IRMS. The enrichment of tracer was measured by monitoring ion masses 2 and 3 to
determine the 2H/1H ratios of myofibrillar protein-bound [2H]-alanine. A series of known
standards were applied to assess the linearity of the mass spectrometer.
4.3.10
Western blot
Sarcoplasmic fractions from biopsy samples collected at 24, 27 at 36 h were prepared as
described above (see 4.3.9 Myofibrillar bound [2H]-alanine enrichment). Aliquots were
defrosted on ice and the protein content determined by colourimetric assay (DC protein assay,
Bio-Rad Laboratories Inc., CA, USA). Following incubation at 95°C for 5 min in XT sample
buffer (Bio-Rad), 20 μL protein per lane was loaded onto 3-8% tris-acetate polyacrylamide
gels (CriterionTM XT, Bio-Rad) and separated by electrophoresis at 150 V for 65 mins in XT
tricine running buffer. Proteins were transferred onto 0.2 µm nitrocellulose membranes using
a Trans-blot turbo transfer system (Bio-Rad), at 2.5 A and 25 V for 10 min. Membranes were
blocked in 5% BSA in TBST (pH 7.6) for 1 h, followed by overnight incubation at 4°C with
rabbit anti-phospho-mTORSer2448 monoclonal antibody (1:1000 in TBST; Cat# 5536, Cell
Signaling Technology Inc., MA, USA; RRID: AB_10691552) and rabbit anti-α-tubulin
(1:15000 in TBST; Cat# 2125, Cell Signaling Technology; RRID: AB_2619646) as a loading
control. Membranes were subsequently washed 3 times in TBST and incubated at 23°C for 60
min in secondary HRP conjugated anti-rabbit IgG antibody (1:3000 in TBST; Cat# ab6721,
Abcam PLC, Cambridge, UK; RRID: AB_955447). Following a 3 x 10 min wash in TBST,
membranes were exposed for 5 min in chemiluminescent substrate solution (ClarityTM, Bio-

135
Rad), visualised using a Chemidoc scanner and analysed using Image Lab software (Bio-Rad)
to quantify band density.
Following detection of phosphorylated mTOR (p-mTOR), membranes were incubated for 15
minutes in Restore stripping buffer (ThermoFisher Scientific), washed in TBST and blocked
for 60 min in 5% BSA in TBST. Membranes were reprobed overnight with an anti-mTOR
monoclonal antibody (1:1000 in TBST; Cat# 2972, Cell Signaling Technology; RRID:
AB_330978) and anti-α-tubulin, and the above steps were repeated to obtain corresponding
bands for mTOR. The expected migrations of p-mTOR, mTOR (both ~289 kDa) and α-tubulin
(~52 kDa) were confirmed using an All-Blue protein ladder (Bio-Rad). Samples were run in
duplicate on each gel and relative abundance was corrected against α-tubulin within each lane.
Finally, the ratio of the relative abundance of p-mTORSer2448 to total mTOR (phospho/total
mTOR ratio) was calculated.
4.3.11
Skeletal muscle mRNA analyses
Total RNA was isolated from ~20 mg frozen muscle tissue using TRI Reagent (ThermoFisher
Scientific) according to the method of Chomczynski and Sacchi (1987). Full details are
provided in Chapter 2. Following spectrophotometric quantification at 260 nm (NanoDrop Lite
Spectrophotometer, ThermoFisher Scientific), first-strand cDNA was synthesised from 2 μg
RNA using SuperScript VILO cDNA Synthesis Kit (Invitrogen, Paisley, UK). A TaqMan
qPCR assay for α1 actin (ACTA1) was performed on every sample in order to verify the
presence of cDNA. Expression levels of 224 target genes selected from PubMed literature
searches and data from our laboratory for their roles in amino acid transport, apoptosis,
substrate metabolism, inflammation, insulin signalling, protein synthesis and breakdown, as
well as several transcription factors, were measured by quantitative real-time PCR using 224-

136
format OpenArray qPCR Plates (ThermoFisher Scientific; full list of analysed genes presented
in Appendix 4). All samples from a given participant were analysed on the same plate alongside
a pooled sample to correct for any variation in reaction efficiency. The relative expression of
each transcript was calculated by the 2-ΔΔCT method, whereby expression was normalised to the
endogenous control genes β2 microglobulin (B2M), α-actin 1 (ACTA1) and β-actin (ACTB) and
each subject’s control leg was used as a comparator value. No significant changes in expression
of endogenous control genes were noted between leg, group or time (Appendix 4). Following
log2 transformation to ensure normal distribution of variance, data were split into an acute
period (i.e., gene expression at 24, 27 and 36 h post-eccentric exercise) and ‘temporal’ period
(i.e., gene expression at 24, 72 and 168 h post-eccentric exercise) and analysed for significant
changes over group, time or time x group. Due to a lack of detectable expression, 10 genes
were omitted from the analysis. Lists of significantly up- or down-regulated genes were
analysed for statistical overrepresentation using the PANTHER classification system (Mi,
Muruganujan, Ebert, Huang, & Thomas, 2019) against pathways defined in PANTHER and
Reactome, as well as against Kyoto Encyclopedia of Genes and Genomes (KEGG) pathways
using DAVID (version 6.8, Laboratory of Human Retrovirology and Immunoinformatics,
Frederick, MD, USA; (Huang da, Sherman, & Lempicki, 2009)). The original gene list, as
opposed to the whole human genome, was used as a background for the enrichment analysis to
eliminate any bias from the selection of genes.
4.3.12
Calculations
Myofibrillar protein fractional synthesis rates (myoFSR) were calculated based on the
incorporation of [2H]-alanine into myofibrillar protein and mean plasma deuterium enrichment
between muscle biopsy time points corrected by a factor of 3.7, based on the deuterium

137
labelling during de novo alanine synthesis. MyoFSR was calculated using the following
precursor-product equation:
𝑚𝑦𝑜FSR (%·h-1 or %·d-1) = ( Em2 – Em1 ) × 100% (4.1)
3.7 × Ep × t
Where Em1 and Em2 are the myofibrillar protein-bound enrichments expressed as mole per cent
excess (MPE), Ep represents mean precursor enrichment between given time points and t is the
time between the corresponding biopsies for which FSR is calculated, expressed as either hours
(h) or days (d).
4.3.13
Statistical analysis
A student’s independent t-test was used to investigate group differences in subject
characteristics and plasma 2H enrichments over the postprandial and overnight periods. A two-
way mixed model analysis of variance (ANOVA; time and group factors) was used to identify
differences within and between treatments for muscle function, peak isokinetic torque, and
daily plasma 2H enrichments. Plasma CK data were log10-transformed prior to analysis by two‐
way mixed model ANOVA (time and group factors) and are presented as back-transformed
geometric mean ± geometric standard deviations (Karlsen et al., 2020). Postprandial and
overnight myoFSR was analysed using a two-way mixed-model ANOVA (leg and group
factors). Muscle mTOR phosphorylation status, muscle-bound [2H]-alanine enrichment and
daily myoFSR were analysed using three-factor mixed model ANOVA (leg, group and time
factors). Where an interaction effect was observed with muscle-bound [2H]-alanine
enrichment, the change over time was assessed by a two-way mixed-model ANOVA (leg and

138
group factors). A Tukey’s multiple comparisons test was applied to locate the individual
differences when a significant main effect of time was detected. Significant interaction effects
were analysed post hoc with Sidak correction for multiple comparisons applied to locate
individual differences. Relative gene expression was analysed using a mixed error-component
model with time and group factors. Separate gene lists were created from genes displaying
significant time, group or interaction effects and manually corrected for multiple comparisons
using the Benjamini-Hochberg procedure (Benjamini & Hochberg, 1995) (false discovery rate
<5%). Hierarchical cluster analysis using Pearson's correlation was subsequently performed on
mean values of genes with significant differential expression (MeV 4.9, TM4) (Saeed et al.,
2003). Statistical analysis was performed using GraphPad Prism 8 (GraphPad Software, Inc.,
San Diego, CA, USA). All data are presented as mean ± SEM unless otherwise stated, with P
< 0.05 indicating statistical significance.
4.4
Results
Participants’ baseline characteristics are shown in Table 4.1. No differences were seen in age,
body mass, height, BMI, or habitual dietary intake between groups. During the 14-day study
period, body mass remained stable and did not differ between groups (PLA: 77.9 ± 4.1 to 77.3
± 4.1; PPB: 73.9 ± 3.9 to 73.8 ± 4.1 kg; baseline to 168 h, respectively) suggesting dietary
compliance. No differences were observed between groups for energy, carbohydrate or fat
consumption during the control diet, but protein intake was significantly greater with PPB (1.2
± 0.0 versus 1.5 ± 0.0 g·kg body mass·d-1, P < 0.001; Table 4.1). At the end of the study,
participants were asked which intervention had been assigned to; upon unblinding, two
participants in PLA and three participants in PPB had correctly identified their group. The
remaining 13 participants either did not know or guessed incorrectly, suggesting effective

139
blinding to the intervention. Skeletal muscle biopsy samples were not obtained from one
participant in PLA, thus plasma deuterium and myofibrillar protein-bound [2H]-alanine
enrichment, myoFSR and mTOR phosphorylation status are determined in n = 8 for this group.
Due to a limited quantity of remaining muscle tissue, gene expression was analysed in n = 7
for both groups.
Eccentric work completed did not differ between PLA and PPB (49160 ± 2542 vs. 44647 ±
3917 J). Peak eccentric torque during set 1 was similar between groups (254 ± 13 and 216 ±
24 n·m; PLA and PPB, respectively). This decreased over time to 182 ± 22 and 157 ± 17 n· m
at set 10 for PLA and PPB respectively (time effect P < 0.001). There was no effect of PPB on
peak eccentric torque.
The matched concentric work performed at 24 h in ECC was 0.6 ± 0.2% and 0.4 ± 0.1% greater
than CON for PLA and PPB, respectively (P < 0.001).
4.4.1
Muscle function
Muscle function in ECC leg expressed relative to CON (%CON) is shown in Figure 4.2A.
Baseline muscle function did not differ between PLA and PPB (104.9 ± 3.3 and 97.4 ± 3.6
%CON, respectively). Following eccentric exercise, muscle function decreased in PLA at 24 h
and remained suppressed until 120 h (69.1 ± 5.3 to 87.5 ± 4.4 %CON, respectively; post hoc P
< 0.05 versus baseline). However, PPB supported the recovery of muscle function (group x
time interaction P < 0.05), with post hoc tests indicating no significant differences compared
to baseline, or between groups, at any time point. Muscle function recovered quicker between
24 – 72 h (8.9 ± 3.6 and 10.8 ± 4.4 %·d-1, PLA and PPB respectively) than between 72 – 168
h post-eccentric exercise (5.4 ± 1.5 and 1.8 ± 1.1 %·d-1; PLA and PPB, respectively; time effect
P < 0.05).
140

141
Figure 4.2. (Overleaf) Markers of muscle damage before (baseline) and every 24 h after
performing 300 maximal, unilateral, eccentric, quadriceps contractions assessed by A: knee
extensor muscle function expressed relative to the contralateral leg (%CON); B: muscle
soreness using 100 mm visual analogue scale (VAS); C: Plasma creatine kinase (CK) levels.
A protein-polyphenol supplement (PPB; n = 9; black circles) or isocaloric placebo (PLA; n =
9; open circles) was consumed daily. A and B presented as means ± standard error; C presented
as geometric mean ± geometric standard deviation displayed on a logarithmic scale on the y-
axis. A: Significant time x group interaction effect (P < 0.05). B: Significant time x group
interaction effect (P < 0.001). C: Significant main effect of time (P < 0.001). Post hoc
differences with time effect denoted by **P < 0.01, ***P < 0.001 significantly different to
baseline. Post hoc differences within time x group interaction effects denoted by: †P < 0.05,
††P < 0.01 significantly different to PLA at same time point; *P < 0.05, **P < 0.01, ***P <
0.001 significantly different to baseline.
Eccentric exercise significantly decreased peak isokinetic torque produced during the function
test (time effect P < 0.001). This decreased from 102.5 ± 3.7 %CON at baseline to 67.0 ± 5.2
%CON at 24 h in PLA. PPB did not influence the loss of peak torque at any time, decreasing
from 96.5 ± 3.4 to 76.8 ± 8.1 %CON from baseline to 24 h (post hoc P < 0.01 versus baseline).
At 48 h, peak torque was 66.8 ± 5.3 %CON in PLA and 82.5 ± 7.7 %CON in PPB (post hoc P
< 0.01 versus baseline), and 74.8 ± 6.4 and 88.0 ± 4.7 %CON in PLA and PPB at 72 h (post
hoc P < 0.05 versus baseline). By 96 h, peak isokinetic torque had recovered to baseline (PLA:
81.8 ± 5.1 %CON; PPB: 95.2 ± 5.3 %CON).
4.4.2
Muscle soreness
Baseline muscle soreness was 2 ± 1 and 0 ± 0 mm in PLA and PPB, respectively (Figure 4.2B).
Muscle soreness rose in PLA at 24 h (post hoc P < 0.01) and peaked at 48 h (post hoc P <

142
0.001) before returning to baseline at 120 h. In PPB, the rise in muscle soreness was
significantly attenuated compared to PLA at 24 h (post hoc P < 0.01) and 48 h (post hoc P <
0.05) and had returned to baseline by 72 h post-eccentric exercise (time x group interaction P
< 0.001).
4.4.3
Plasma creatine kinase
Baseline plasma CK levels (Figure 4.2C) were 153 ± 2 and 125 ± 2 U·L-1 for PLA and PPB
respectively. Plasma CK rose equally in both groups (time effect P < 0.001) and remained
elevated at all timepoints post-eccentric exercise (post hoc P < 0.01). PPB was not significantly
different from PLA at any time point.
4.4.4
Plasma precursor enrichment
Plasma deuterium enrichment (Figure 4.3A) reached 0.61 ± 0.04% at 24 h in PLA and was
similar in PPB (0.57 ± 0.03%). Daily plasma enrichment remained stable and did not differ
between groups (7-day average of 0.62 ± 0.01% and 0.57 ± 0.01% in PLA and PPB,
respectively). Between 24 to 27 h, and 27 to 36 h post-eccentric exercise, enrichment did not
differ between PLA and PPB (24 to 27 h: 0.61 ± 0.03% and 0.57 ± 0.02%; 27 to 36 h: 0.63 ±
0.03% and 0.58 ± 0.02%; PLA and PPB, respectively).
143
Figure 4.3. A: Daily plasma 2H enrichment (%) following oral 2H2O ingestion in participants
consuming a protein-polyphenol beverage (PPB; n = 9; black circles) or isocaloric placebo
(PLA; n = 8; open circles). B: Enrichment of myofibrillar bound [2H]-alanine (MPE) in skeletal
muscle biopsy samples obtained 24, 27, 36, 72 and 168 h after performing 300 maximal
eccentric quadriceps contractions in one leg (ECC) or contralateral control leg (CON). Inset
are data expressed relative to a linear scale on the x-axis to demonstrate an increase of
enrichment with respect to time. For myofibrillar bound [2H]-alanine enrichment, significant
main effect of time (P < 0.001) and leg (P < 0.001) for all comparisons. Between 27 – 36 h,
significant interaction for time x leg (P < 0.01) and time x leg x group (P < 0.05). Post hoc
differences within time x leg x group interaction effect denoted by: ##P < 0.01 change from
previous timepoint significantly greater in ECC versus CON leg in PPB.
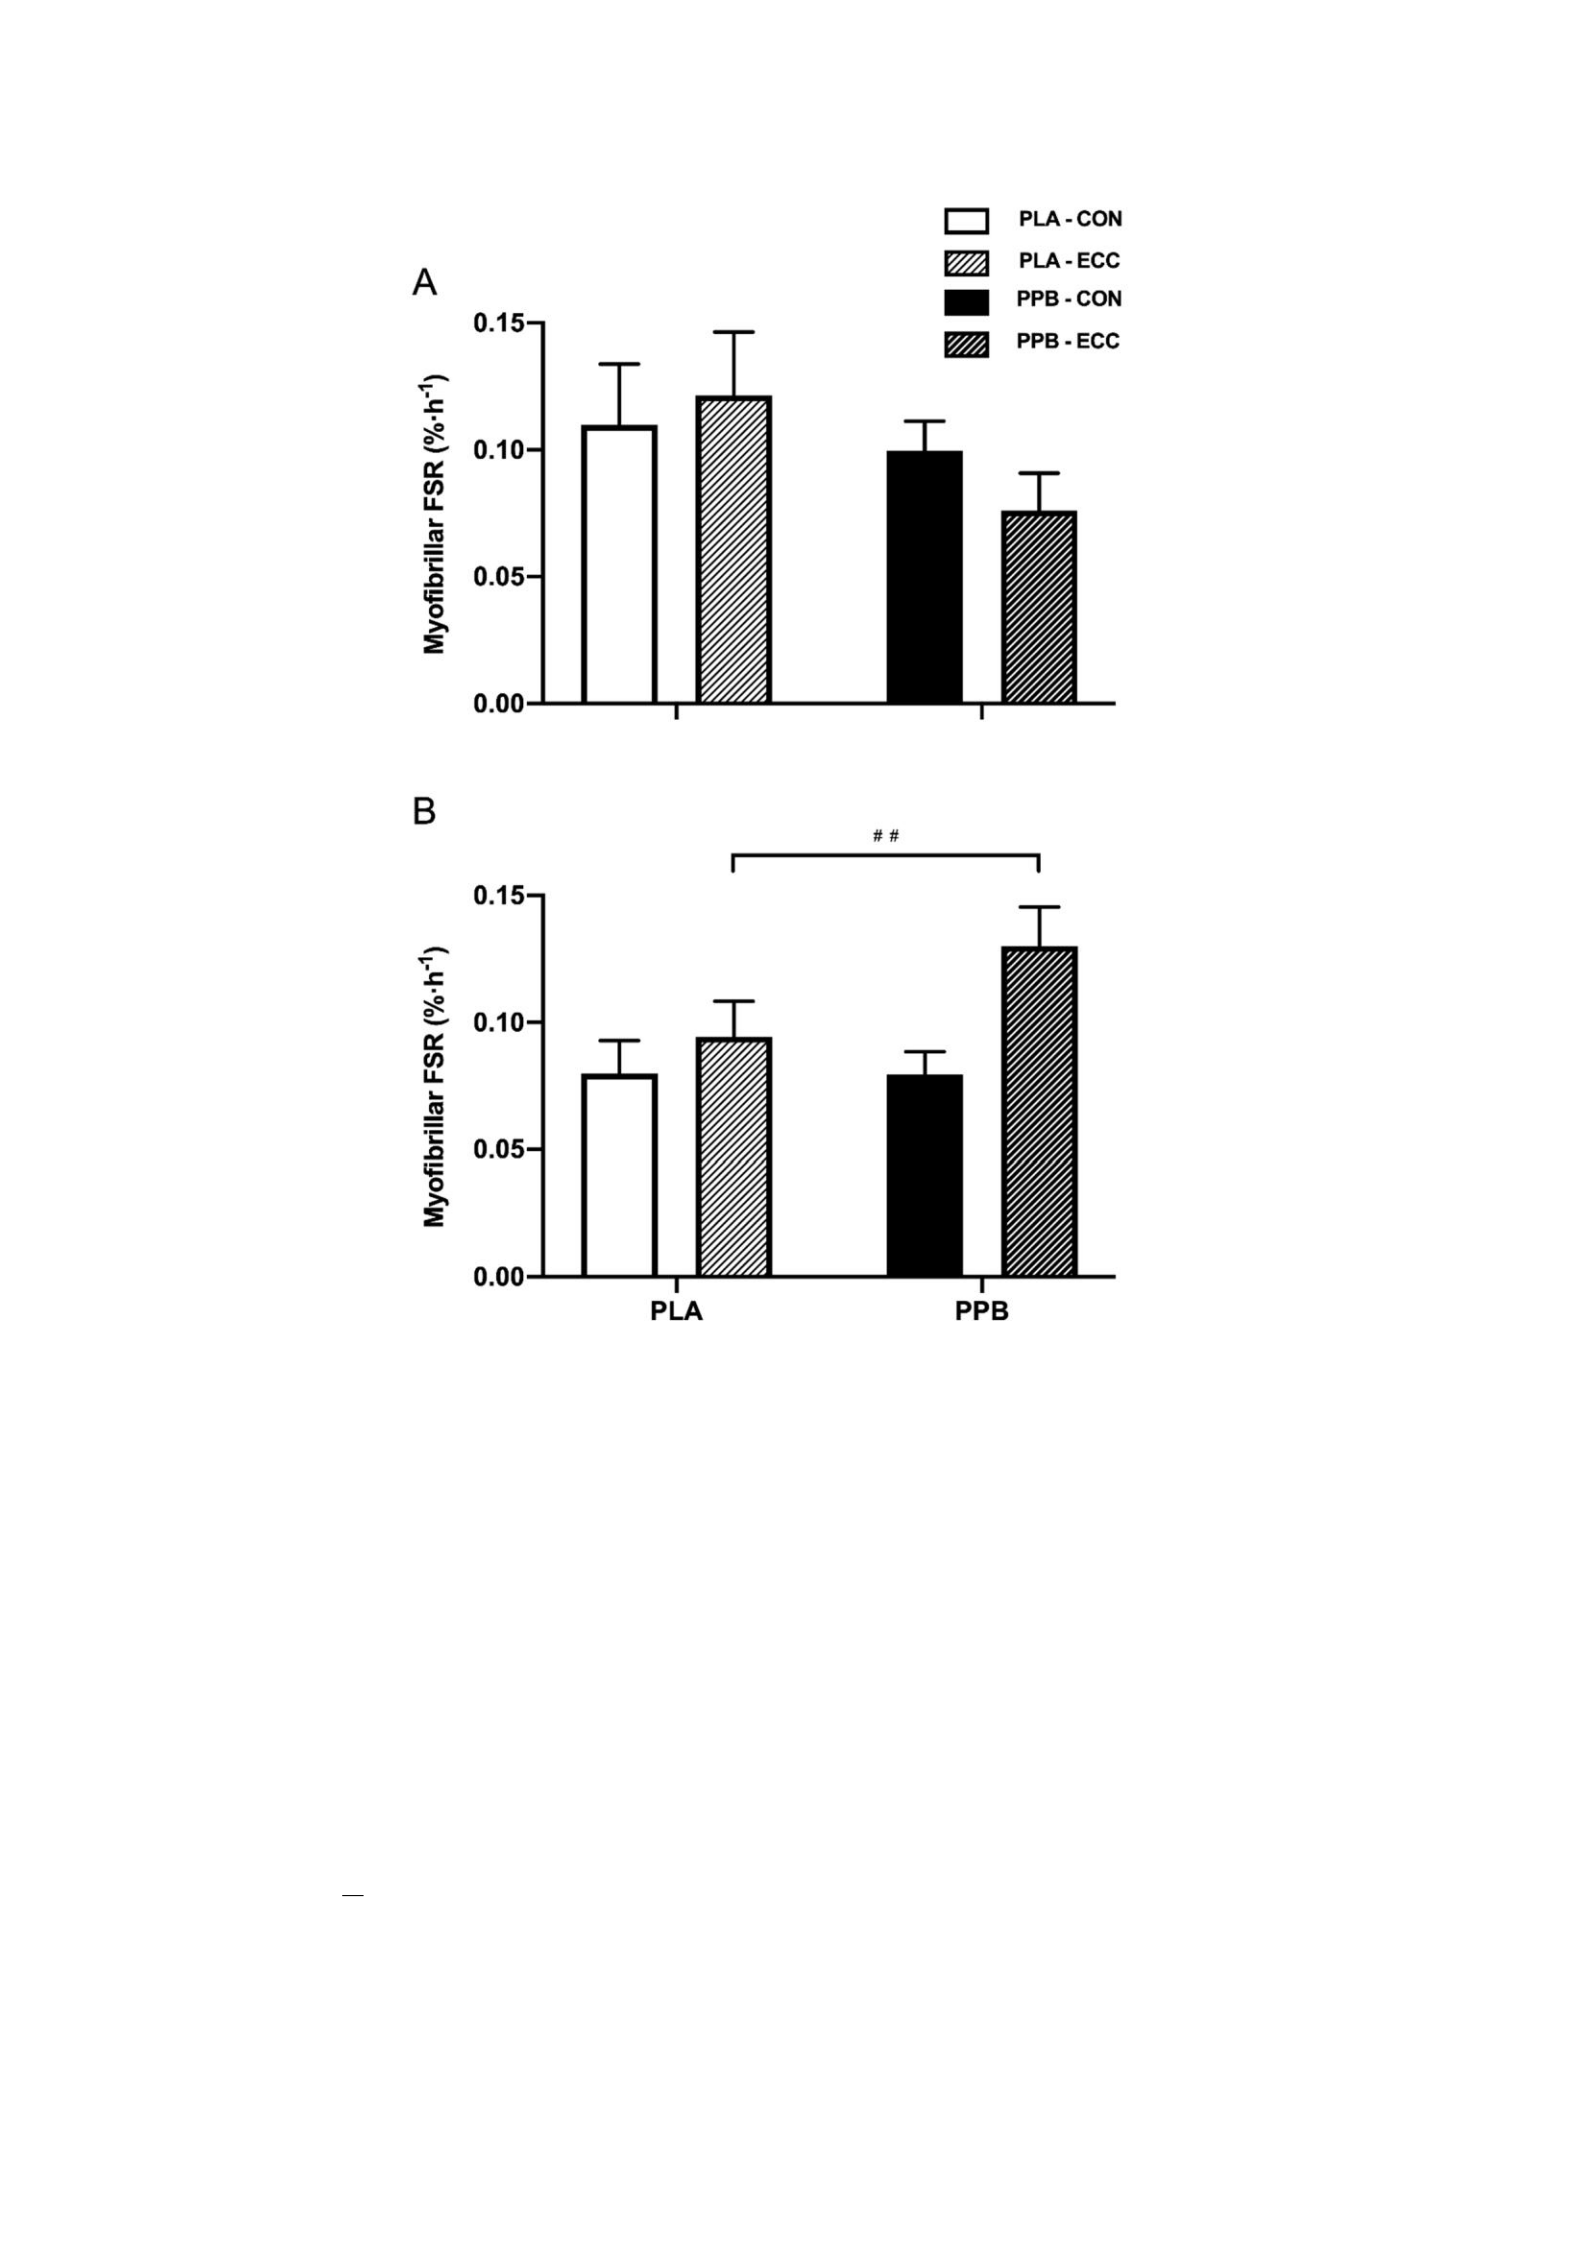
144
Figure 4.4. Myofibrillar protein fractional synthesis rate (FSR; expressed as %·h-1) over A: a
3 h postprandial period following maximal, bilateral, isokinetic, concentric exercise and the
consumption of a post-exercise protein-polyphenol supplement (PPB; n = 9; black bars) or
isocaloric placebo (PLA; n = 8; white bars); and B: the subsequent 9 h overnight period,
beginning with the consumption of a maltodextrin beverage. Postprandial and overnight
periods correspond to between ~24 - 27 h and ~27 - 36 h after 300 maximal eccentric
quadriceps contractions in one leg (ECC; hashed bars). The contralateral control leg is
represented as CON (solid bars). Fractional synthetic rates calculated from plasma deuterium
enrichment as precursor pool. Significant main effect of leg (i.e., CON vs ECC; P < 0.01;
denoted by ##).

145
4.4.5
Myofibrillar protein enrichment and fractional synthesis rates
Myofibrillar protein-bound [2H]-alanine enrichments (Figure 4.3B) increased over the
postprandial period 24 to 27 h after eccentric exercise (time effect P < 0.001) and were 32.5 ±
6.6% and 29.4 ± 4.6% higher in ECC versus CON at 24 and 27 h, respectively, in PLA (leg
effect P < 0.001). A similar response was seen in PPB whereby MPE was higher in ECC versus
CON by 26.5 ± 3.9% and 20.5 ± 3.6% at 24 and 27 h, respectively. Overnight, the increase in
myofibrillar protein-bound [2H]-alanine enrichments in PLA was similar for CON (26.9 ±
3.9%) and ECC (24.3 ± 4.3%) legs. However, with PPB, the increase was greater in ECC (29.4
± 2.1%) than in CON (22.1 ± 2.5%; time x leg x group interaction P < 0.05). Between 72 – 168
h, myofibrillar protein-bound [2H]-alanine enrichments increased by 86.4 ± 8.1% in CON and
by 71.3 ± 12.5% in ECC for the PLA group (time effect P < 0.001). PPB increased by a similar
extent, by 109.5 ± 21.2% and by 93.1 ± 7.0% in CON and ECC, respectively. Enrichment in
the ECC leg was 23.1 ± 5.6 and 20.6 ± 6.8% greater than CON for PLA and PPB at 72 h, and
14.3 ± 9.9 and 13.9 ± 5.5% greater in ECC than CON for PLA and PPB at 168 h (leg effects P
< 0.001). Data were analysed for linearity whereby a straight-line model was preferred to
explain the increase in enrichment over time (r2 = 0.794), indicating that a rise to plateau was
not evident.
Postprandial and overnight myoFSR is displayed in Figure 4.4. Following exercise at 24 h,
postprandial (24 – 27 h) myoFSR was unaffected by group or prior eccentric exercise.
Overnight (27 – 36 h) myoFSR was greater in ECC vs. CON (PLA: 0.094 ± 0.013 vs. 0.080 ±
0.012; PPB: 0.130 ± 0.008 vs. 0.080 ± 0.008 %·h-1; leg effect P < 0.01), where the difference
between legs in PPB (76 ± 25%) tended to be greater than the difference in PLA (33 ± 19%;
leg x group interaction P = 0.06).
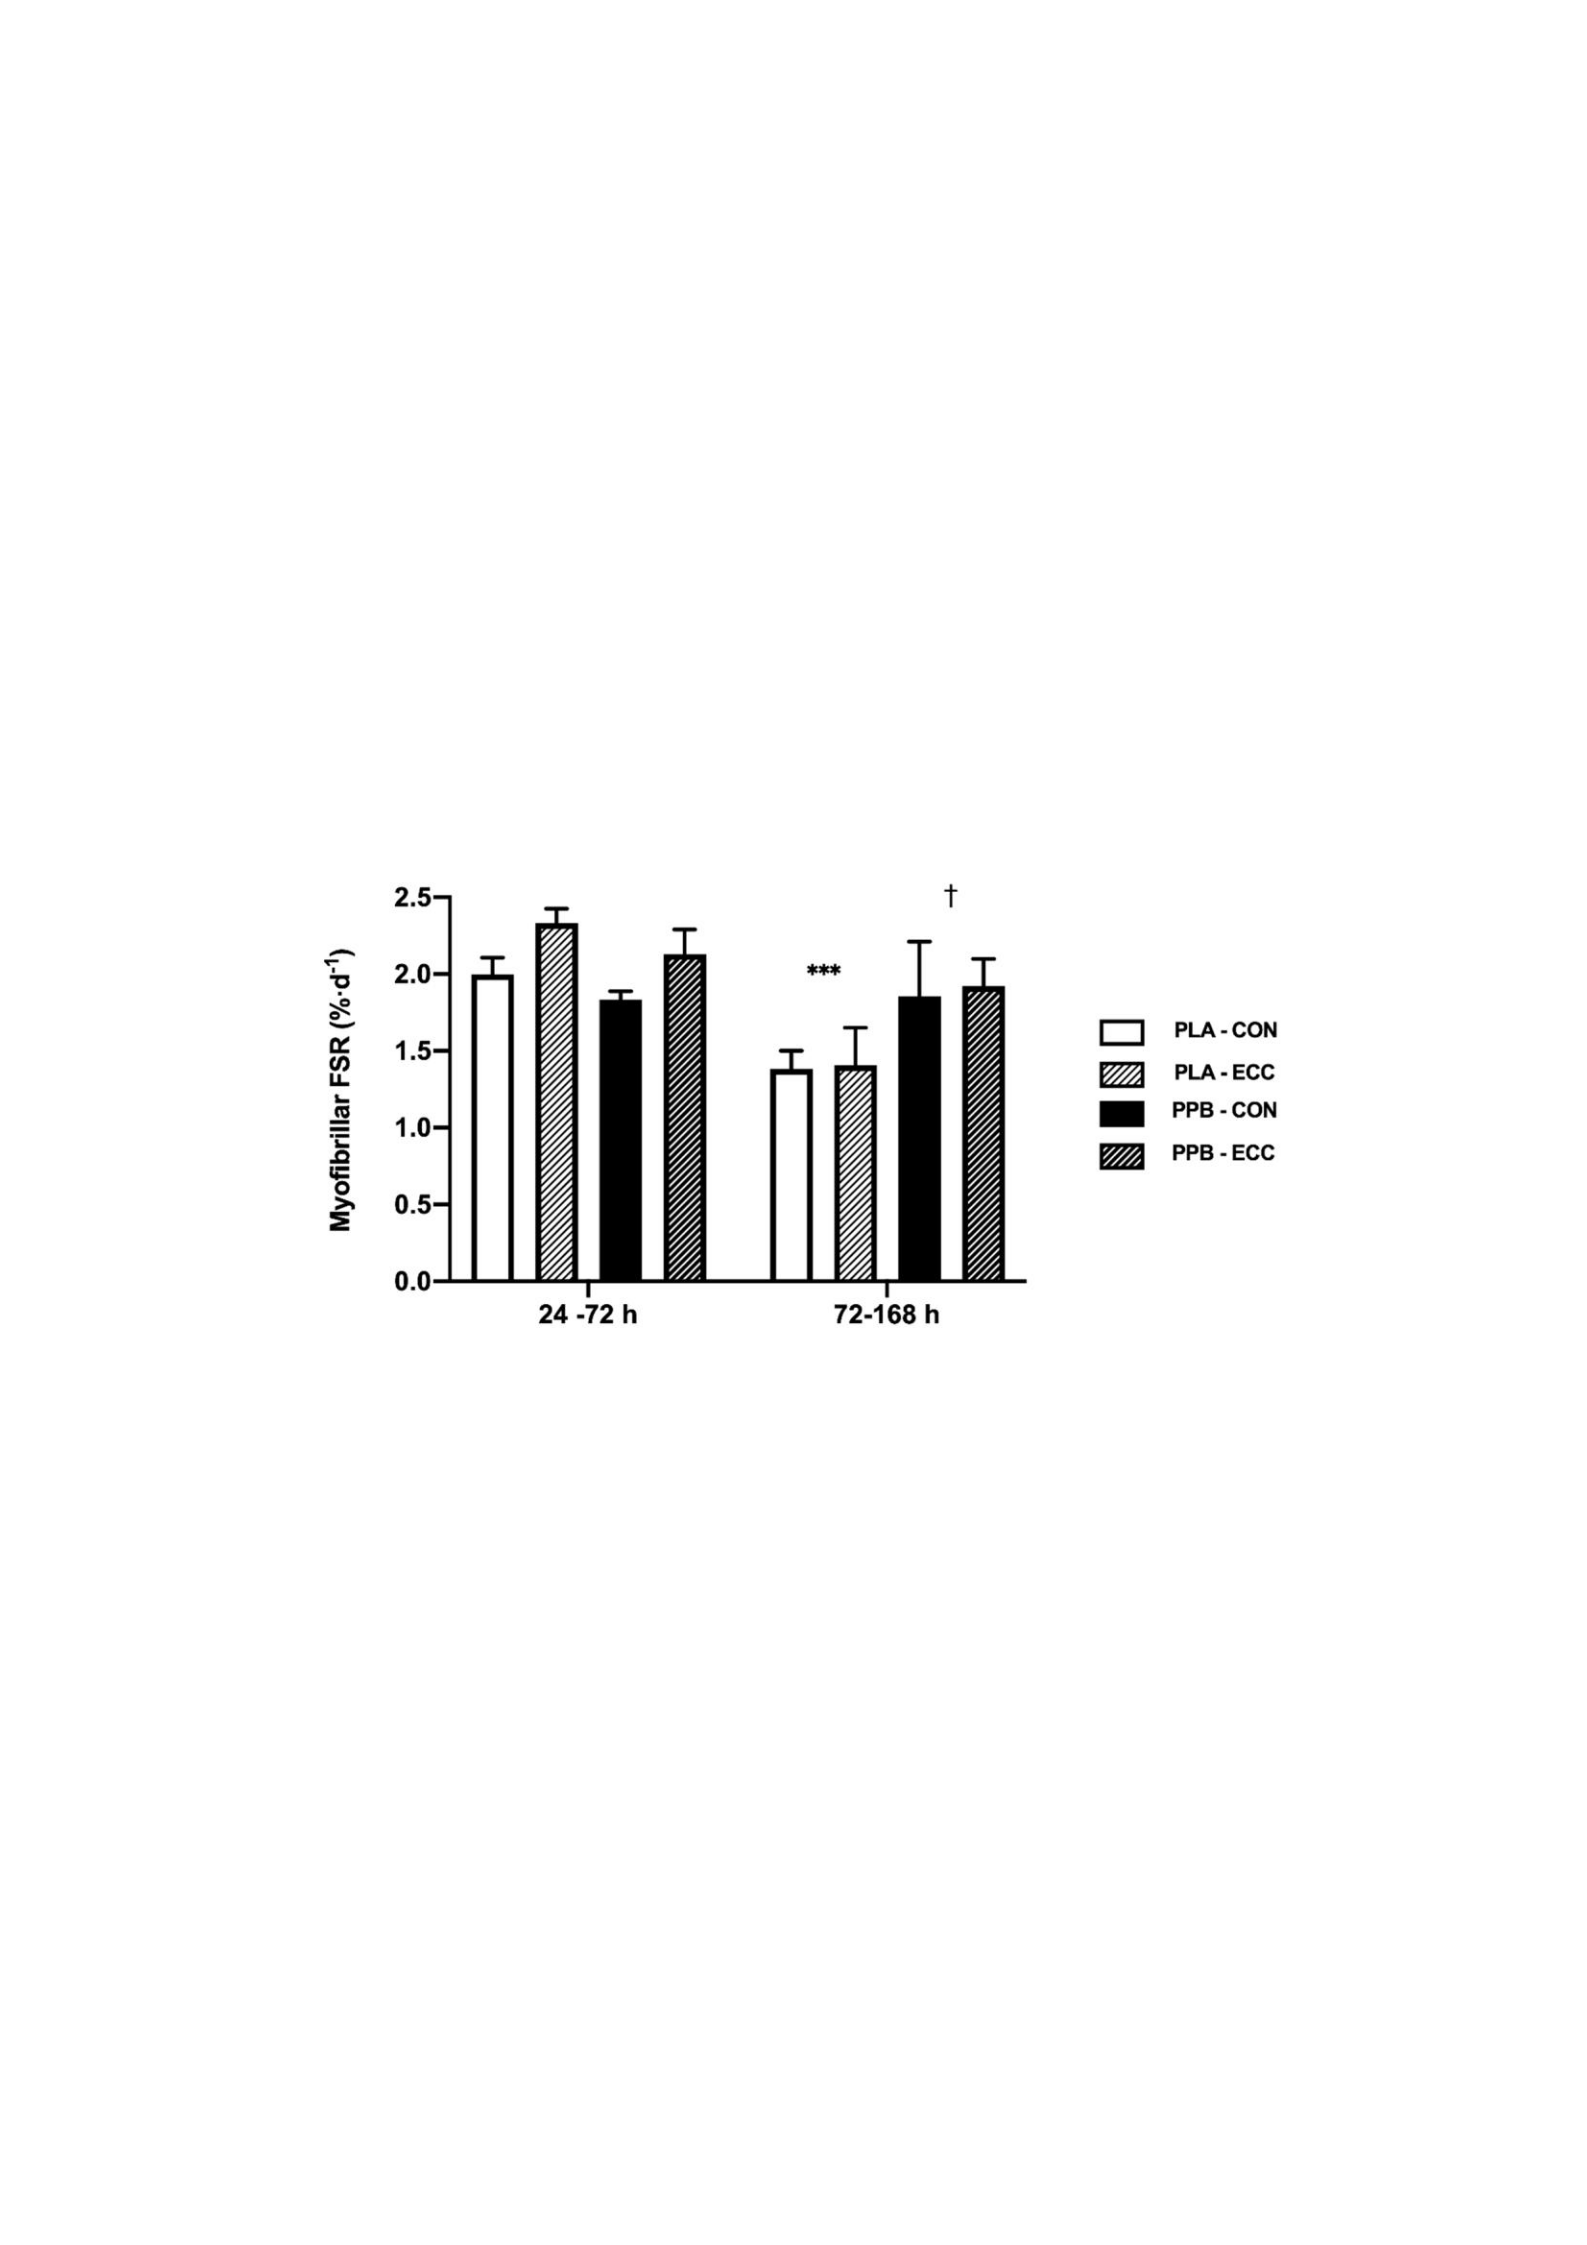
146
Daily myoFSR (Figure 4.5) fell from 24 – 72 h to 72 – 168 h in PLA (CON: 2.00 ± 0.10 to
1.38 ± 0.11; ECC: 2.33 ± 0.09 to 1.41 ± 0.23 %·d-1; respectively; post hoc P < 0.001).
Conversely, daily myoFSR remained unchanged in PPB from 24 – 72 h to 72 – 168 h (CON:
1.83 ± 0.05 to 1.86 ± 0.34; ECC: 2.13 ± 0.15 to 1.92 ± 0.17 %·d-1; respectively; group x time
interaction P < 0.05) and was significantly greater than PLA between 72 - 168 h (post hoc P <
0.05). MyoFSR tended to be 16.0 ± 6.6% higher in ECC than in CON (leg effect P = 0.06).
Figure 4.5. Free-living, cumulative myofibrillar protein fractional synthesis rate (FSR;
expressed as %·d-1) between 24 – 72 h and 72 – 168 h of recovery from 300 maximal, unilateral,
eccentric contractions and consumption of a post-exercise protein-polyphenol supplement
(PPB; n = 9) or isocaloric placebo (PLA; n = 8). Eccentric exercise was performed in one leg
only (ECC). The contralateral control leg is represented as CON (solid bars). Fractional
synthetic rates calculated from plasma deuterium enrichment as precursor pool. Significant
time x group interaction effect (P < 0.05). Post hoc differences within time x group interaction
effect denoted by: †P < 0.05 significantly different to PLA at same time point; ***P < 0.001
significantly different to 24 – 72 h in PLA.
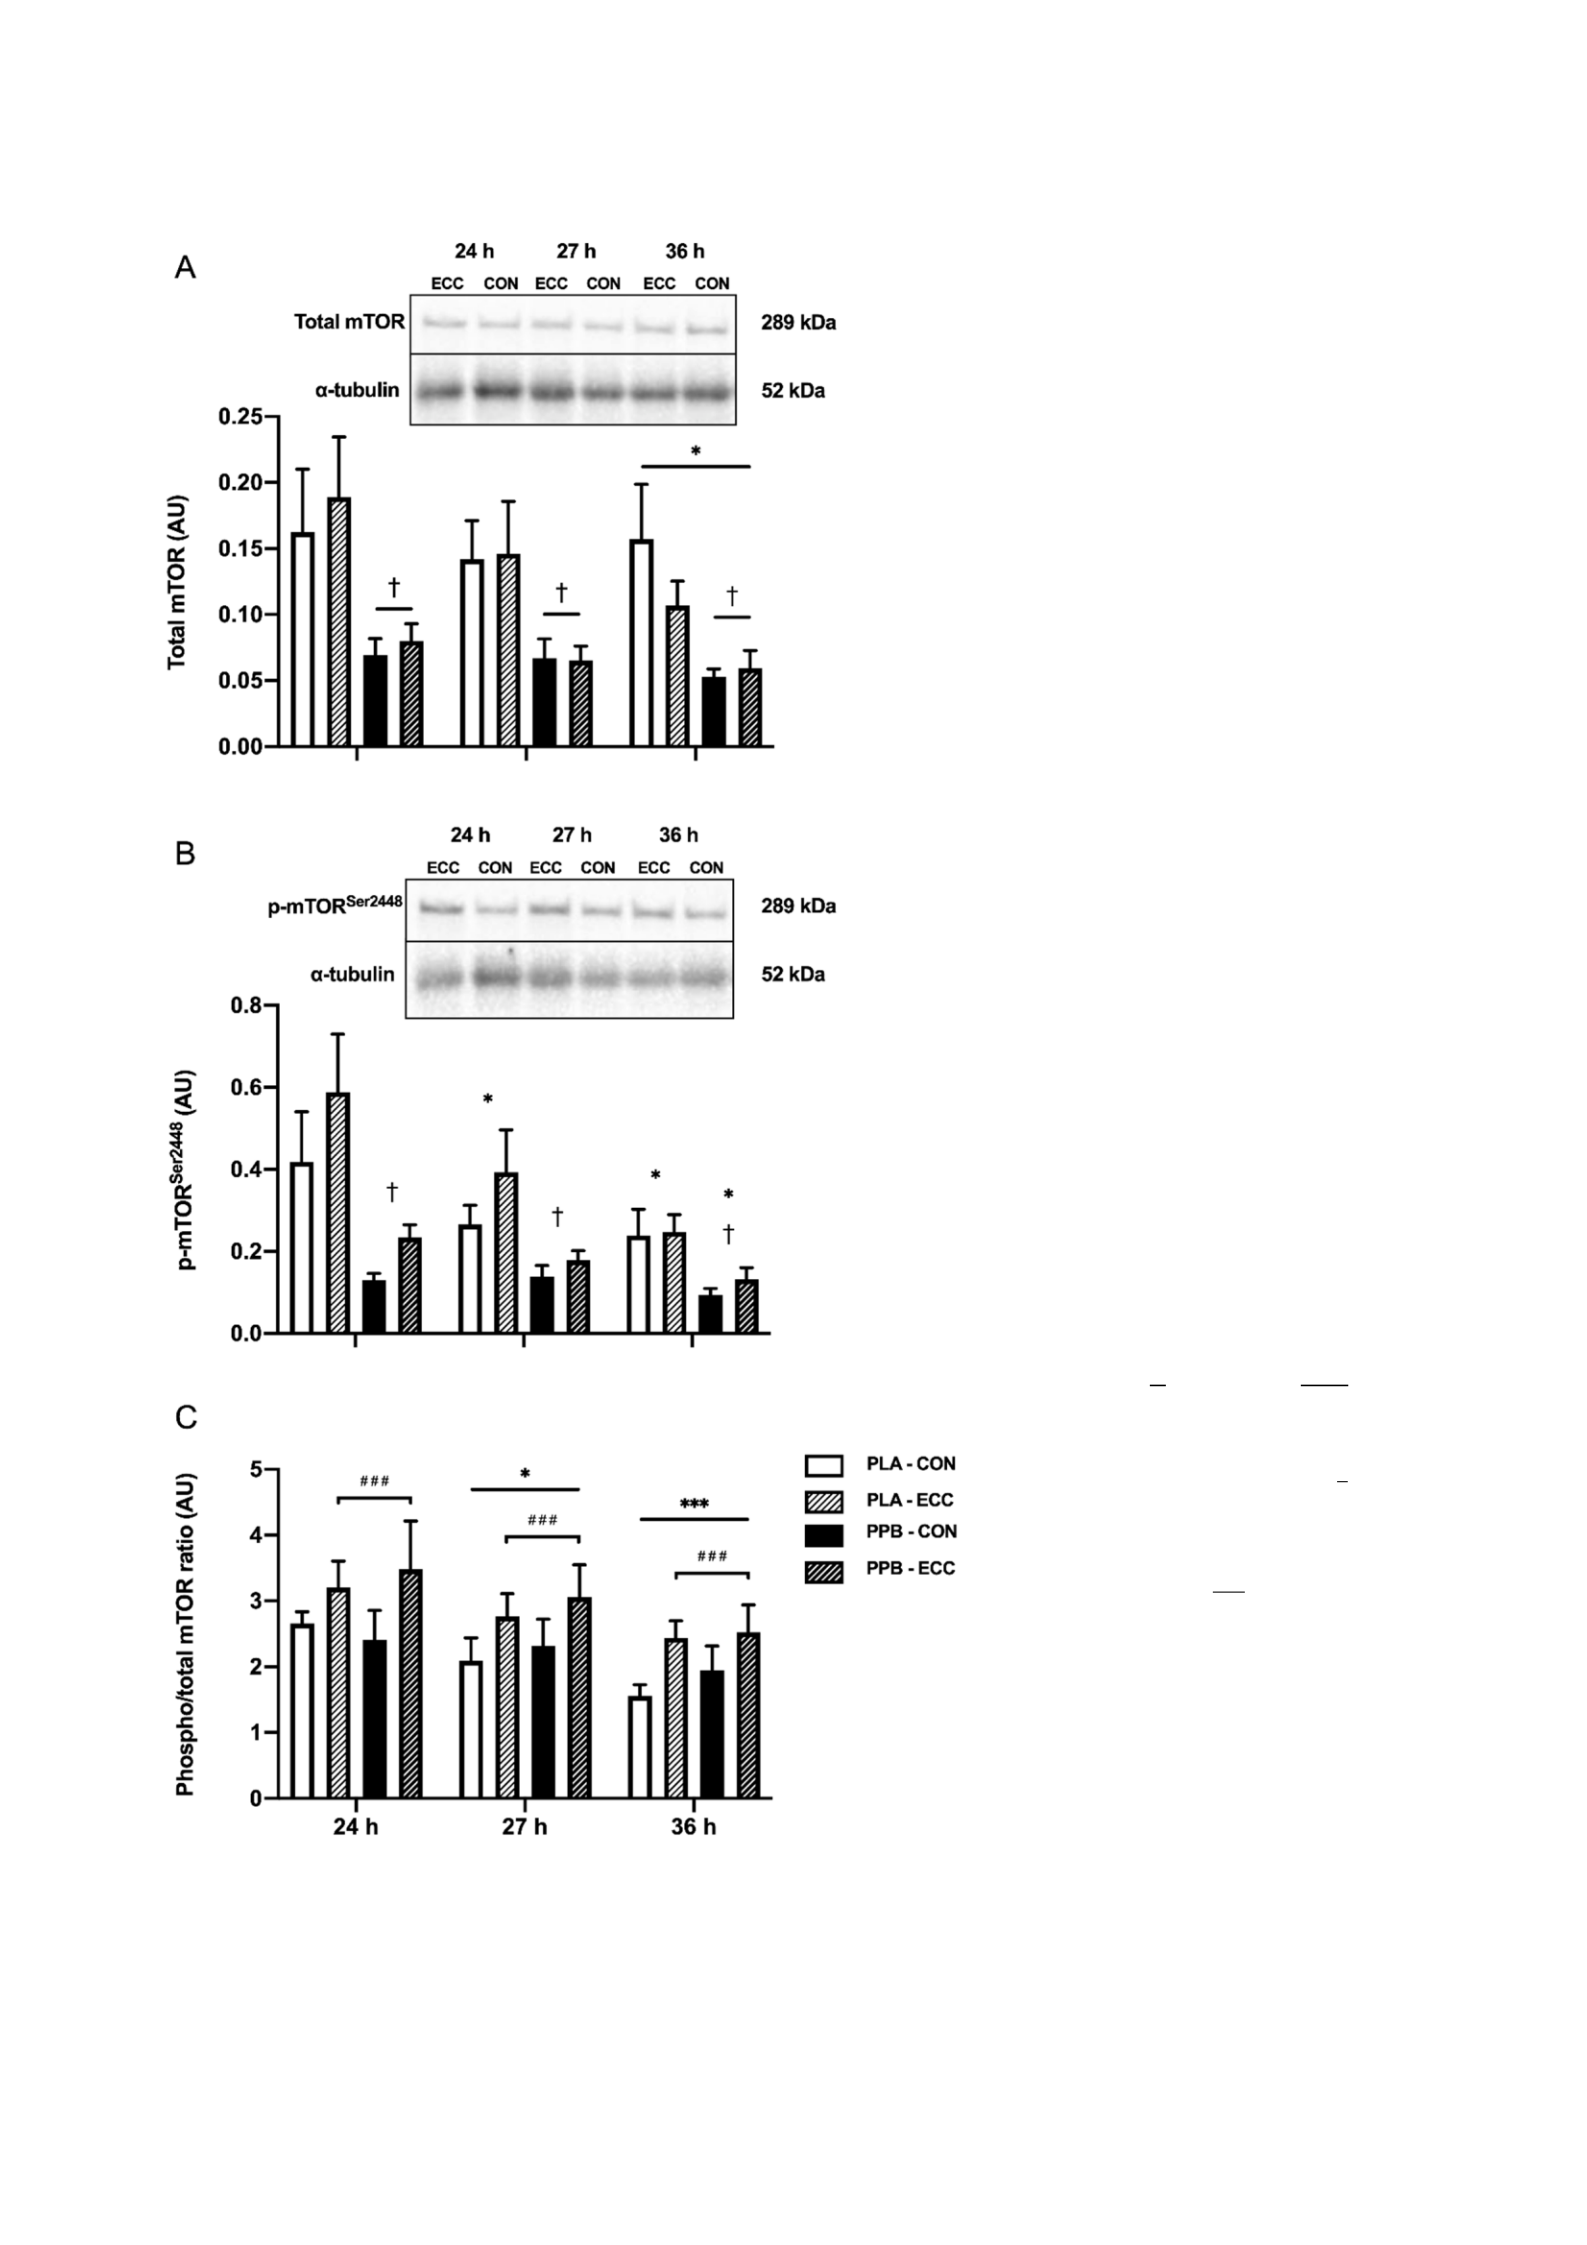
147
Figure 4.6. Western blot of. A:
Total mTOR protein; B: mTOR
phosphorylated at Ser2448 (p-
mTORSer2448); and C: the ratio
of phosphorylated to total
protein; in an eccentrically
exercised leg (ECC) and
contralateral control (CON).
Protein-polyphenol supplement
(PPB; n = 9) or isocaloric
placebo (PLA; n = 8) was
consumed after 24 h. A:
Significant main effects of time
(P < 0.05) and group (P < 0.05).
B: Significant main effect leg
(P < 0.001). Significant time x
group interaction effect (P <
0.05). C: Significant main
effect of time (P < 0.001) and
leg (P < 0.001). Post hoc
differences in time effect
denoted by *P < 0.05, ***P <
0.001, significantly different to
baseline; group denoted by †P <
0.05 significantly different to
PLA; and leg ###P < 0.001
significantly different to CON.
Post hoc differences in time x
group interaction effect
denoted by: †P < 0.05
significantly different to PLA
at same time point; *P < 0.05
significantly different to
baseline.

148
4.4.6
mTOR protein content and phosphorylation status
Total mTOR protein content fell between 24 and 36 h (time effect P < 0.05) and was lower in
PPB than PLA (group effect P < 0.05; Figure 4.6A). In ECC, p-mTORSer2448 protein content
was 55 ± 17% and 100 ± 34% higher than CON in PLA and PPB respectively (leg effect P <
0.001; Figure 4.6B). In PLA, this fell at 27 and 36 h from 24 h (group x time interaction P <
0.05; post hoc P < 0.05) and in PPB was lower at 36 h than 24 and 27 h (post hoc P < 0.05).
Skeletal muscle phospho/total mTOR ratio fell over the 24 – 27 h postprandial and 27 – 36 h
overnight period (Figure 4.6C; time effect P < 0.001). The phospho/total mTOR ratio in ECC
leg was 40 ± 6% and 49 ± 13% higher than CON in PLA and PPB, respectively (leg effect P <
0.001). No group difference was evident.
4.4.7
Gene expression
Expression of 22 genes changed between 24, 27 and 36 h post-eccentric exercise (Figure 4.7;
Appendix 4.1; FDR <5%). Hierarchical cluster analysis revealed two distinct clusters; mean
expression values for 18 genes were positive, indicating relatively greater expression in ECC
compared to CON, and mean expression values of four genes were negative, indicating lower
expression in ECC compared to CON. Analysis against the Reactome pathway database
highlighted enrichment of six different pathways, with ‘Regulation of RUNX2 expression and
activity’ (UBC, CUL1 and PPARGC1A), ‘MAP3K8 (TPL2)-dependent MAPK1/3 activation’
(UBC, CUL1 and NFKB1), ‘Signaling by NOTCH4’ (UBC, CUL1 and SMAD3), ‘TNFR2 non-
canonical NF-kB pathway’ (UBC, CUL1 and TNFRSF12A) and ‘Regulation of PLK1 Activity
at G2/M Transition’ (UBC and CUL1) the most significant (P < 0.05). Gene functional analysis
highlighted no enriched pathways against PANTHER and KEGG databases.
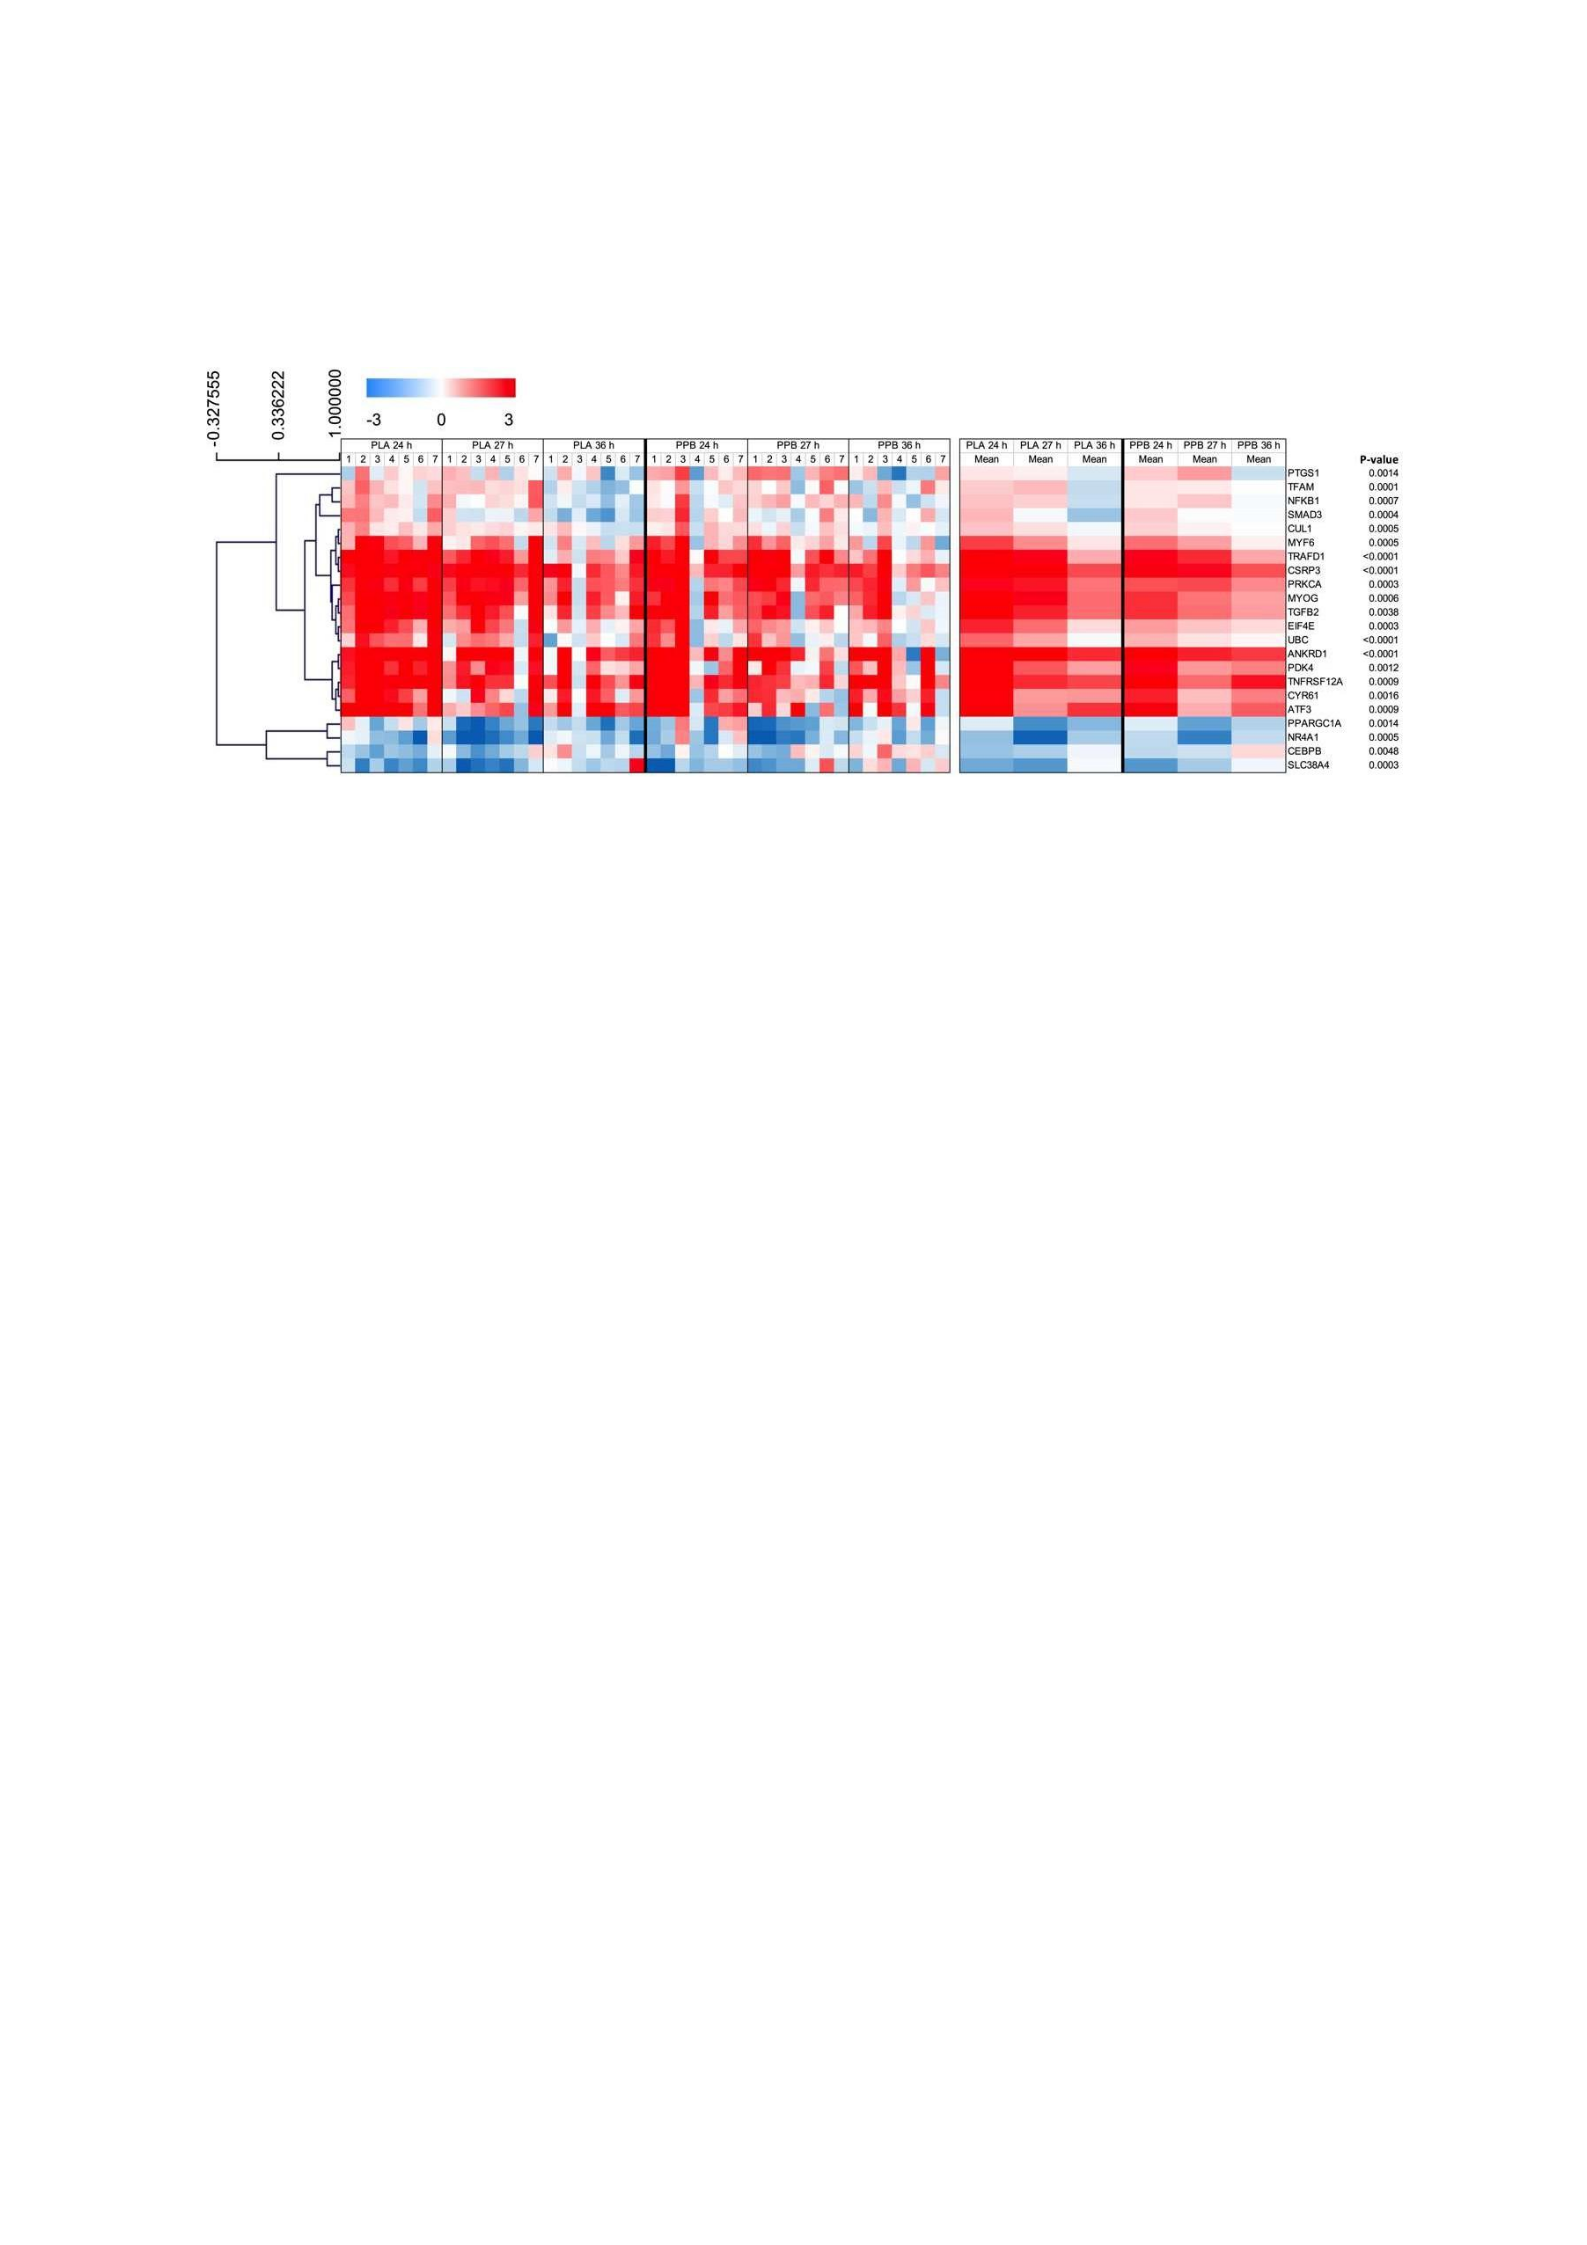
149
Figure 4.7. Heatmap with hierarchical clustering of differentially expressed skeletal muscle
transcripts from pathways involved in amino acid transportation, apoptosis, substrate
metabolism, inflammation, insulin signalling, protein synthesis and breakdown, as well as
several transcription factors. Skeletal muscle biopsies were taken 24, ~27 and ~36 h after
performing 300 maximal, unilateral, eccentric, quadriceps contractions, corresponding to pre,
~3 h and ~12 h after maximal, bilateral, concentric exercise and consumption of a post-exercise
protein-polyphenol supplement (PPB; n = 7) or isocaloric placebo (PLA; n = 7). All individual
values are expressed as fold change from control leg at the same timepoint, with log2
transformation applied. Heatmap constructed from genes showing significant main effects for
time, with the corresponding P-value, as assessed by a mixed error-component model with time
and group factors and satisfying criterion for false discovery rate (FDR) <5%. Hierarchical
clustering performed on mean data using Pearson’s correlation.
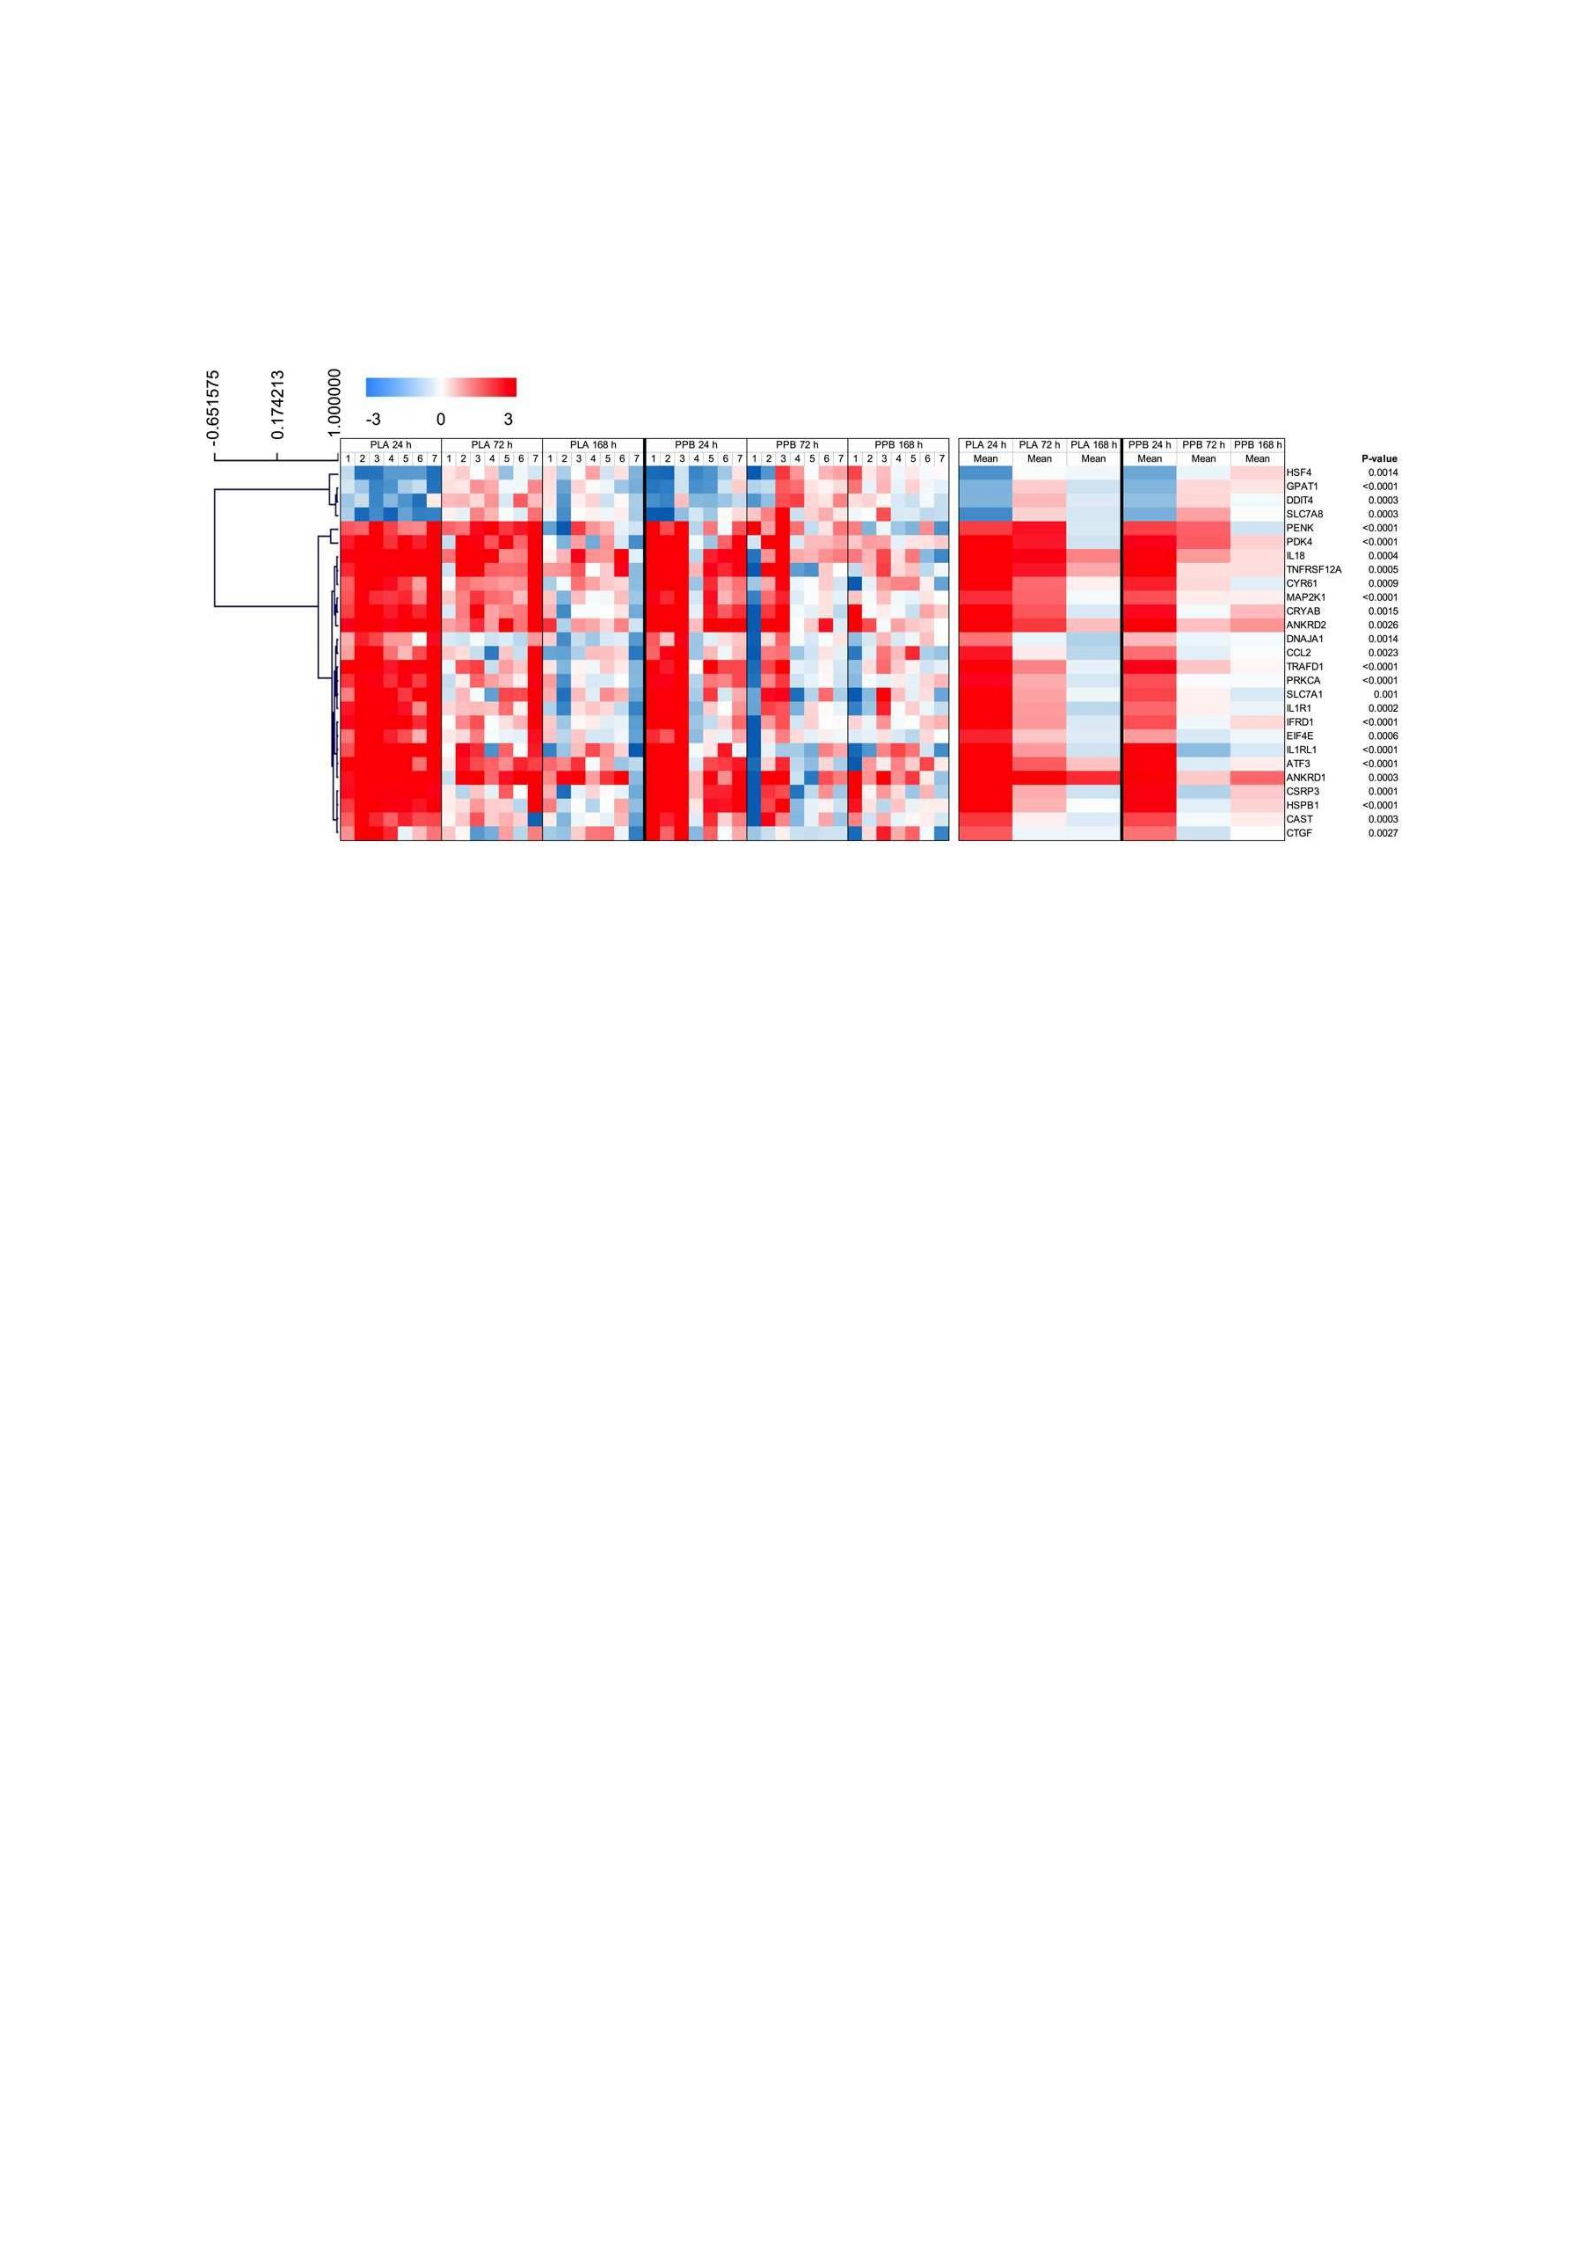
150
Figure 4.8. Heatmap with hierarchical clustering of differentially expressed skeletal muscle
transcripts from pathways involved in amino acid transportation, apoptosis, substrate
metabolism, inflammation, insulin signalling, protein synthesis and breakdown, as well as
several transcription factors. Skeletal muscle biopsies taken in the rested state 24, 72 and 168
h after performing 300 maximal, unilateral, eccentric, quadriceps contractions with daily
maximal, bilateral, concentric exercise and consumption of a post-exercise protein-polyphenol
supplement (PPB; n = 7) or isocaloric placebo (PLA; n = 7). All individual values are expressed
as fold change from control leg at the same timepoint, with log2 transformation applied.
Heatmap constructed from genes showing significant main effects for time, with the
corresponding P-value, as assessed by a mixed error-component model with time and group
factors and satisfying criterion for false discovery rate (FDR) <5%. Hierarchical clustering
performed on mean data using Pearson’s correlation.

151
Three genes (ACTN3, IL1RL1, FOXO3) were differentially expressed between PLA and PPB
(P < 0.05) and a further seven genes (TFAM, PLIN2, CCL8, CTSL1, EIF4E, EIF4EBP1,
GDF11) exhibited a leg by group interaction effect (P < 0.05), but these did not satisfy the
criterion for FDR <5% so were not analysed for enriched pathways.
Expression of 27 genes changed between 24, 72 and 168 h post-eccentric exercise (Figure 4.8;
Appendix 4.2; FDR <5%). Hierarchical cluster analysis revealed two distinct clusters; mean
expression values for 23 genes were positive and decreased over time, whereas mean
expression values for four genes were negative and increased over time. Gene functional
analysis highlighted no enriched pathways against Reactome, PANTHER or KEGG databases.
Two genes (ATF3, IL1B) were differentially expressed between PLA and PPB (P < 0.05) and
six genes (CCL8, HK2, DGAT2, PIK3R1, TRAF6 and GDF11) showed a leg by group
interaction (P < 0.05). However, these did not satisfy the criterion for FDR <5% so were not
analysed for enriched pathways.
4.5
Discussion
The present study aimed to characterise, for the first time, the time course of rates of MyoPS
and key gene expression pathways of inflammation, protein synthesis, proteolysis and substrate
metabolism over a week of recovery following voluntary eccentric muscle contractions in
humans. To deduce the relative importance of MyoPS, we utilised a protein and polyphenol
nutritional intervention targeted at improving functional recovery whilst fully controlling for
diet and strenuous exercise. As expected, the post-exercise provision of 20 g protein combined
with 650 mg pomegranate extract accelerated the recovery of muscle function by 120 h and
suppressed soreness over 48 h following muscle damage compared to an isocaloric placebo in
a healthy population. Remarkably, the nutritional intervention improved recovery at 48 h when

152
the loss of muscle function and soreness was the greatest in the placebo group (~36% decline
in muscle function). However, a major finding of the present study, and contrary to our
hypothesis, was that this improvement in recovery was not underpinned by an increase the rate
of daily MyoPS compared to placebo between 24 – 72 h, when the loss of muscle function and
recovery rate was the greatest, despite a trend for elevated overnight MyoPS during this time.
This would suggest that exogenous amino acid availability is not limiting to MyoPS from 24 h
after damaging exercise, perhaps due to increased endogenous availability from protein
breakdown (Biolo et al., 2002; Phillips et al., 1997). To this end, MyoPS may already be
maximal during this period such that further stimulation is not possible, or elevated MyoPS
may only be required for a short period of time to enhance recovery. Furthermore, the
upregulation in inflammatory and regenerative signalling following eccentric exercise was not
affected by the nutritional intervention, suggesting that accelerated recovery is not caused by
the transcriptional regulation of some inflammatory and regenerative pathways.
Eccentric exercise caused a profound loss in muscle function (~ 34% below baseline at 24 h)
persisting for 120 h in the placebo group. Additionally, eccentric exercise caused ~27%
decrease in peak isokinetic torque produced during the muscle function assessment, in
agreement with previous reports (Draganidis et al., 2017; Michailidis et al., 2013; Paulsen et
al., 2007). This was observed together with ~35% greater phospho/total mTOR ratio, ~41%
greater rates of overnight MyoPS and a tendency for elevated rates of daily MyoPS in the
damaged versus control leg between 24 – 72 h and 72 – 168 h following eccentric exercise.
Thus, by showing an accompanying, transient loss of muscle contractile ability as demonstrated
in the present study, we support and extend upon existing data demonstrating that the repair
and remodelling process after muscle damage is associated with elevated rates of MyoPS and
mTOR phosphorylation (Damas et al., 2016b; Moore et al., 2005). Furthermore, consistent
with human models of muscle damage induced by eccentric exercise (Draganidis et al., 2017;

153
Farup et al., 2014a; Michailidis et al., 2013; Paulsen et al., 2010; Vissing et al., 2008), we show
that muscle soreness peaked after 48 h and was followed by a rise in plasma CK (Figure 4.2B
and C) between 96-168 h after eccentric exercise (Paulsen, Mikkelsen, Raastad, & Peake,
2012b). In the present study, nutritional intervention accelerated the recovery of muscle
function by 120 h, more so than has been reported with either whey protein alone (72 h) (Cooke
et al., 2010) or milk protein blends (48 h) (Cockburn et al., 2008; Draganidis et al., 2017).
Although the recovery of peak isokinetic torque was only qualitatively similar, function was
designated our primary marker of contractile ability as this likely reflects both peak torque and
fatigability, which are known consequences of damage to contractile elements with eccentric
exercise (Jones, Newham, & Torgan, 1989). This, in addition to the composition of the
nutritional intervention and the strict dietary control employed to remove the influence of a
variable habitual diet on amino acid availability, may explain the difference in magnitude of
recovery that was observed with PPB compared to previous work. Indeed, a small but
favourable effect for whey protein supplementation on the recovery of function up to 96 h after
resistance exercise was highlighted in a recent meta-analysis, of which only three of eight
studies analysed controlled for dietary protein intake (Davies et al., 2018). Furthermore,
polyphenol-rich pomegranate extract alone improves recovery of muscle function in humans
by ~9-11% 48 h following eccentric exercise (Trombold et al., 2010; Trombold et al., 2011),
which may have an additive or synergistic effect when combined with protein to drastically
improve the rate of muscle recovery.
To our knowledge, no study to date has determined whether an increase in MyoPS is
responsible for an improvement in recovery following damaging eccentric exercise in humans.
Despite significantly accelerating recovery of muscle function by 120 h, and contrary to our
hypothesis, rates of postprandial MyoPS were not enhanced following nutritional intervention.
Furthermore, phospho/total mTOR ratio at 24, 27 and 36 h after eccentric exercise was similar

154
between groups, as were rates of daily MyoPS between 24 and 72 h when the greatest
difference in recovery was observed. Taken together, these data are not consistent with MyoPS
being the primary mechanism dictating muscle recovery. Whilst it is conceivable that
nutritional intervention would not be sufficient to provide an anabolic stimulus, we are
confident this was not the case as the provision of 20 g protein containing 2 g leucine has been
demonstrated to stimulate a robust muscle protein synthetic response over the effects of
exercise alone (Moore et al., 2009a; van Vliet et al., 2017). Given that the rates of postprandial
MyoPS in the present study (~0.101 %·h-1) are comparably larger than have previously been
reported following nutrition (~0.088 %·h-1) (Wilkinson et al., 2015) or nutrition with exercise
(~0.082 %·h-1) (Davies et al., 2019), and that myofibrillar protein synthesis plateaus despite
increasing amino acid availability in healthy individuals (Witard et al., 2014), we propose that
exogenous amino acids are not limiting to MyoPS at this time. The proximity of the evening
meal and/or the breakdown of endogenous proteins following eccentric exercise (Lowe et al.,
1995; Phillips et al., 1997) and injury (Biolo et al., 2002) may provide sufficient substrate for
MyoPS. While we are unable to simultaneously characterise rates of muscle protein breakdown
with the application of 2H2O as described herein, greater rates of muscle protein breakdown
would increase the availability of amino acids for both synthesis and outward transport (Biolo
et al., 2002). As a result, this may increase amino acid delivery to both ECC and CON legs,
thus accounting for the similar rates of synthesis. Moreover, should rates of muscle protein
breakdown subside thereafter as is reported elsewhere (Lowe et al., 1995; Phillips et al., 1997),
amino acid availability may then become limiting to MyoPS. This would explain our and
others’ (Wilkinson et al., 2014) observations of a drop in daily MyoPS between 72 – 168 h
following eccentric exercise in the absence of additional protein. Consistent with this proposed
mechanism, the provision of exogenous protein likely afforded greater rates of MyoPS during
this later period compared to placebo (Figure 4.5).

155
At the beginning of the overnight period (27 h), phospho/total mTOR ratio decreased by ~13%
compared to the postprandial period (24 h). While the direct determination of mTOR activity
by assessing kinase activity and/or investigating the phosphorylation status of additional
downstream targets would have extended our mechanistic insight, these data are supported by
a ~24% decrease in rates of MyoPS overnight in the control leg. Together, it appears that the
protein synthetic response was not maximal overnight, in accordance with previous work
(Beelen et al., 2008). As previously discussed, we identified greater overnight MyoPS in the
eccentrically exercised versus control leg, which may be due to increased amino acid
availability from protein breakdown (Lowe et al., 1995; Phillips et al., 1997). Accordingly,
should amino acid availability dictate rates of MyoPS overnight, the protein bolus ~3 h prior
and greater daily protein intake may explain why MyoPS tended to be greater still following
nutritional intervention (~18% greater with eccentric exercise alone versus ~64% greater with
eccentric exercise and nutritional intervention). This suggests the existence of a key window
within 36 h after eccentric exercise, in which basal or overnight MyoPS can be manipulated to
accelerate recovery. Nonetheless, this did not manifest as a difference in daily MyoPS between
24 - 72 h, and so overnight differences may be negligible when accounting for all periods of
protein synthesis 24 h after eccentric exercise. Furthermore, severe muscle-damaging protocols
in mice appear to delay the rise in protein synthesis for more than 48 h (Lowe et al., 1995) and
so the existence of this window requires further investigation.
To identify changes in pathway signalling during the recovery period, we analysed the
expression of 224 genes selected for their roles in amino acid transportation, apoptosis,
substrate metabolism, inflammation, insulin signalling, protein synthesis and breakdown, as
well as several transcription factors (Appendix 4.1). Prior eccentric exercise augmented
inflammatory signalling over the postprandial and overnight time frames between 24 and 36 h
following eccentric exercise, in agreement with previous transcriptomic analyses (Hyldahl et

156
al., 2011; Mahoney et al., 2008; Thalacker-Mercer, Dell'Italia, Cui, Cross, & Bamman, 2010).
This was evidenced by enrichment of ‘TNFR2 non-canonical NF-kB pathway’ and ‘MAP3K8
(TPL2)-dependent MAPK1/3 activation’, as well as clustering of PTGS1, NFKB1, TRAFD1,
TNFRSF12A and CYR61 demonstrating upregulated expression in the eccentrically exercised
leg relative to the control leg. Common to all pathways enriched over this time was the
expression of CUL1, a component of the SKP1-CUL1-F-box (SCF) E3 ligase complex, and
UBC, a ubiquitin precursor protein, which promotes NFκB signalling through SCF-mediated
ubiquitination of the NFκB inhibitor, IκB (Chen, 2005). Interestingly, CUL1 and UBC
clustered closely with TGFB2, and to a lesser extent SMAD3 (Figure 4.7), which promote SCF
complex ligase activity and have been demonstrated to arrest cell-cycle progression through
ubiquitination of CDC25A (Ray et al., 2005). Indeed, mitogen-activated protein kinase
(MAPK) signalling has an additional role in cell cycle regulation (Chambard, Lefloch,
Pouyssegur, & Lenormand, 2007) and has been identified as a transcriptionally active
biological process following a similar eccentric exercise protocol in humans (MacNeil, Melov,
Hubbard, Baker, & Tarnopolsky, 2010). With concurrent enrichment of ‘Regulation of PLK1
Activity at G2/M Transition’, these data identify cell cycle regulation being transcriptionally
relevant during recovery (Ray et al., 2005), in support of previous work (MacNeil et al., 2010).
Specifically, this time course approach reveals signalling related to the inhibition of cell cycle
progression and elevated inflammation that was initially upregulated and proceeded to fall over
the postprandial and overnight phase (Figure 4.7). Given these analyses were performed on
whole muscle homogenates, we cannot be sure of the definitive origin of such genes.
Nonetheless, these may emanate from populations of mitotic cells that are known to proliferate
in response to eccentric exercise, such as satellite cells (Mikkelsen et al., 2009). In support, we
also identified the expression of two markers of myogenic differentiation within the CUL1 and
UBC cluster: MYF6 and MYOG (Figure 4.7). Together with clustering of PRKCA, EIF4E and

157
CSRP3, this signature is indicative of a regenerative milieu in the skeletal muscle following
eccentric exercise, corroborating our observations of elevated overnight MyoPS and
phosphor/total mTOR ratio in the eccentrically exercised leg.
To increase the temporal understanding of muscle recovery processes, and account for
circadian regulation of gene expression following muscle damage (Zaaqoq et al., 2019), we
performed separate bioinformatic analysis on muscle biopsy samples collected at 24, 72 and
168 h (Appendix 4.2). Here, continued expression and clustering of genes associated with
inflammatory (IL18, TNFRSF12A, CYR61, ILR1 and IL1RL1) and regenerative (EIF4E,
IFRD1, PRKCA, MAP2K1 and CSRP3; Figure 4.8) signalling was evident, as was identified
over the acute period. Specifically, these genes support a role for NFκB signalling beyond a 3
h period following eccentric exercise as previously identified (Hyldahl et al., 2011). Although
only the expression of the NFκB subunit 1 (NFKB1) was identified over the acute period
(Figure 4.7), the expression of up- and down-stream genes data together with our ontology
analysis between 24 and 36 h after eccentric exercise implicate this pathway as being relevant
throughout the recovery process. Indeed, NFκB appears to positively regulate myogenesis
following injury via the non-canonical NFκB pathway involving TNFRSF12A (Enwere et al.,
2012; Enwere, Lacasse, Adam, & Korneluk, 2014), and by increasing MAPK signalling
through TNF-α (Chen et al., 2005). This process may be further regulated by IFRD1
expression, in part through suppressing the canonical NFκB subunit p65 and enhancing MyoD
signalling, and thereby potentiating myogenesis following injury (Micheli et al., 2011).
Interestingly, in the present study, CCL2 expression was ~4.8-fold greater at 24 h than 168 h,
which is required for macrophage/monocyte infiltration and myofibrillar repair in vitro (Lu et
al., 2011). Within this cluster of genes, we also show expression of HSPB1 and CRYAB heat
shock proteins, which are known to co-localise with damaged myofibrillar structures between

158
48 and 168 h following eccentric-exercise-induced muscle damage (Paulsen et al., 2007) and
are positively associated with muscle protein accretion (Paulsen et al., 2012a).
By capturing transcriptional events across multiple timepoints together with measures of
muscle function, we extend on previous findings that identify transcriptional changes at single
timepoints 3 – 48 h into recovery (Hyldahl et al., 2011; Mahoney et al., 2008; Thalacker-Mercer
et al., 2010), and support the roles of upregulated inflammatory and regenerative signalling,
potentially mediated by NFκB, as being relevant to the restoration of muscle function following
damage (Figure 4.7). Nonetheless, despite expediting muscular recovery following eccentric
exercise, we show no effect of nutritional intervention on the expression of any transcripts over
either acute or temporal time frames that satisfied the criterion for FDR <5%. In spite of this,
a small number of transcripts were observed to be affected by nutritional intervention with
significance at the level of P < 0.05 (Appendix 4) but were discounted from the present analysis
due to the necessity to control for type I errors. Of these, IL1RL1 expression appeared ~84%
lower with nutritional intervention over the acute period, consistent with attenuation of NFκB
signalling. Accordingly, IL1B and ATF3, up- and down-stream of NFκB respectively, were
~69% and ~56% lower with nutritional intervention across the temporal timeframe. Thus,
targeted analysis into NFκB signalling may be of interest to explore a possible relationship
with accelerated recovery.
Very limited data exist investigating MyoPS or signalling pathways in cases where targeted
interventions, such as protein or polyphenol supplementation, have accelerated recovery, and
to our knowledge, no studies that show a beneficial effect of such interventions on muscular
recovery utilise comprehensive measures of MyoPS or investigate changes in signalling at the
transcriptional level. Whilst the contribution of cytosolic protein synthesis to recovery remains
unknown, we determined mTOR phosphorylation status in a cytosolic protein portion and
determined rates of MyoPS to investigate the recovery of contractile elements and investigated

159
associated gene signalling pathways. Therefore, the present data suggest that synthesis of
myofibrillar proteins and gene signalling pathways may not limit muscular recovery under
normal physiological conditions in humans. Indeed, eccentric exercise has been routinely
demonstrated to increase intramuscular leukocyte infiltration in human (Draganidis et al., 2017;
Paulsen et al., 2010) and animal models (Pizza et al., 2005). In particular, leukocyte infiltration
(Paulsen et al., 2010), specifically that of neutrophils (Pizza et al., 2005), appears to attenuate
recovery of muscle function ~24 h after the initial injury and in rare instances induces
‘secondary damage’ to the surrounding tissue tissues through the release of reactive oxygen
species (ROS) and proteolytic enzymes (Nathan, 2006), manifesting as a reduction in
contractile ability ~24 h after the initial injury (MacIntyre et al., 1996; Paulsen et al., 2010).
Various polyphenols have been reported to have free radical scavenging ability in vivo and
disrupt signalling of the NADPH oxidase pathway, thereby reducing ROS production (Maraldi,
2013). In human neutrophils stimulated ex vivo by lipopolysaccharide, treatment with a
polyphenol extract rich in proanthocyanins significantly reduced the release of proteinases and
levels of ROS (Michel et al., 2019). In animal models, inhibition of such pathways reduces the
prevalence of damaged myofibers by ~76% after stretch-induced injury (Brickson et al., 2003).
Supporting this possible mechanism, recent work showed that acceleration of muscle function
with whey protein is associated with lower circulating protein carbonylation, despite similar
degrees of leukocyte infiltration in the muscle (Draganidis et al., 2017). Interestingly in the
present study, whilst not satisfying the criterion for FDR <5%, CCL8 appeared to be ~72%
lower at 24 h with nutritional intervention, suggesting possible reductions in monocyte
infiltration following eccentric exercise, rather than suppression of activity. Moreover,
proanthocyanidins suppress skeletal muscle neutrophil content following contusion injury in
rats, whilst leaving macrophage numbers unaffected (Myburgh et al., 2012). Thus, the
combination of whey protein and pomegranate extract in the nutritional intervention employed

160
in the present study may have influenced neutrophil numbers and/or activity, thereby
accelerating muscle recovery. Whilst investigating this mechanism was beyond the scope of
our current investigation, this warrants further attention, particularly in the first 24 h following
eccentric exercise where considerable leukocyte infiltration is evident (Paulsen et al., 2010).
In conclusion, utilising a specific protein-polyphenol nutritional intervention targeted at
increasing myofibrillar protein synthesis and suppressing inflammation improves muscle
function recovery by 120 h and suppresses soreness over 48 h following maximal eccentric
exercise. We show for the first time that this acceleration in recovery occurs in the absence of
elevated rates of postprandial myofibrillar protein synthesis. Overnight rates of myofibrillar
protein synthesis tended to be greater with nutritional intervention, suggesting that a critical
recovery window may occur within 36 h post damaging exercise. However, this was not
reflected by greater daily rates between 24 – 72 h when muscle function loss was the greatest
and as such these data are not consistent with myofibrillar protein synthesis being the primary
mechanism dictating muscle recovery. Transcriptional analysis revealed initial upregulation of
inflammatory and regenerative signalling following eccentric exercise, which was maintained
during the recovery of muscle function. Nonetheless, nutritional intervention did not influence
gene expression in these pathways, suggesting that transcriptional regulation of some
inflammatory and regenerative pathways does not underpin recovery from skeletal muscle
damage.

161
Chapter 5 - Protein-Polyphenol Nutritional Intervention Increases Rates of
Daily Myofibrillar Protein Synthesis and Promotes Muscle Functional
Gains following the onset of a Resistance Training Program.

162
5.1
Abstract
Resistance exercise training (RET) increases myofibrillar protein synthesis rates, but the
contribution of this process toward training adaptations is unclear. Healthy males and females
consumed a twice-daily protein-polyphenol intervention (PPB; n=15) targeted at increasing
rates of myofibrillar protein synthesis (MyoPS), or an isocaloric placebo (PLA; n=14) over 30
sessions of unilateral RET. Muscle strength and function were measured in trained (T) and
untrained (U) legs pre, post and throughout training, with fibre cross-sectional area (fCSA)
measured pre and post. Rates of MyoPS obtained over 48 h following the onset of training
using deuterated water were significantly greater with PPB (2.01 ± 0.15 versus 1.51 ± 0.16
%·d-1, pooled across leg, P < 0.05). After 10 sessions (3.0 ± 0.1 weeks) of training, muscle
function was increased by PPB only (PLA: 102.6 ± 3.9 %U pre-training to 100.8 ± 2.4 %U at
session 10; PPB: 99.9 ± 1.8 %U pre-training to 107.2 ± 2.4 %U session 10; time x group
interaction P < 0.05). After 30 sessions, RET increased muscle strength (P < 0.05) and function
(P < 0.01) by 9.6 ± 5.7% and 9.4 ± 4.9% respectively in PLA, with no additional effect of PPB
(8.4 ± 3.8% and 14.0 ± 5.6% increase in strength and function, respectively). Type II fCSA
increased with PPB only (group x time interaction P < 0.05). These data provide a novel insight
into the time course of resistance training adaptations, showing that nutritional strategies
increasing MyoPS accelerate the early functional improvements during resistance-type
exercise training and increase type II fibre hypertrophy.

163
5.2
Introduction
A period of resistance-type exercise training (RET) accrues skeletal muscle proteins and
increases muscle strength (Lemon et al., 1992; MacDougall, Elder, Sale, Moroz, & Sutton,
1980; Mayhew, Kim, Cross, Ferrando, & Bamman, 2009). In both animal (Goldberg, 1968;
Laurent et al., 1978) and human (Brook et al., 2015) models of hypertrophy, the expansion in
muscle size aligns with greater rates of muscle protein synthesis. Acutely, muscle contraction
stimulates muscle protein synthesis disproportionately to the increase in muscle protein
breakdown (Biolo et al., 1995b; Phillips et al., 1997). Furthermore, contraction regulates
mTORC1 activity and protein synthesis through MAPK/ERK signalling pathways (Figure 1.2)
(Aronson et al., 1997; Williamson, Gallagher, Harber, Hollon, & Trappe, 2003), and increases
expression of Pax7 and MyoG, markers of satellite cell activation and differentiation (Burd et
al., 2010b). Recent genome-wide transcriptome analysis, using a within-person design to
reduce heterogeneity in RET outcomes, highlighted that several regulators of muscle protein
synthesis correlate with muscle hypertrophy (Stokes et al., 2020). Together, these data suggest
that muscle protein synthesis is the key process mediating adaptations to RET.
Providing exogenous amino acids after resistance exercise increases skeletal muscle amino
acid uptake and stimulates rates of MPS, creating net positive protein balance (Biolo et al.,
1997; Tipton et al., 1999). Specifically, ~88% of phenylalanine synthesised following
resistance exercise is derived from circulation when fed versus ~45% when fasted (Biolo et al.,
1995b; Biolo et al., 1997). Accordingly, greater protein intakes during RET are positively
associated with greater muscle strength, lean body mass and muscle fibre size gain in young,
healthy individuals training for > 6 weeks (Cermak et al., 2012; Morton et al., 2018). For
example, milk protein ingestion following resistance exercise increases amino acid availability
and confers a greater muscle protein synthetic response versus isonitrogenous soy or
isoenergetic carbohydrate (Tang et al., 2007; Wilkinson et al., 2007). When consumed over 12

164
weeks of RET, milk protein either post-exercise or before sleep promotes greater increases in
lean mass and muscle fibre cross-sectional area (fCSA) versus carbohydrate or noncaloric
placebo (Hartman et al., 2007; Snijders et al., 2015).
At present, a paucity of data exists directly linking the myofibrillar protein response to RET
adaptations, so the relationship between myofibrillar protein synthesis (MyoPS) and RET
remains largely circumstantial. Moreover, the magnitude of MyoPS measured following the
onset of RET appears unrelated to resultant hypertrophy and strength gains (Damas et al.,
2016b; Mayhew et al., 2009; Mitchell et al., 2014), and instead is considered reflective of
muscle damage induced by unaccustomed exercise (Damas et al., 2018; Damas et al., 2016b).
Nonetheless, the greatest gains in strength are observed over the first 3 weeks of RET (Brook
et al., 2015; Hakkinen et al., 1998) when rates of myofibrillar protein synthesis are highest
(Brook et al., 2015). However, due to a lack of intervention studies directly manipulating
MyoPS, the role in moderating RET adaptations, particularly over the first 3 weeks, remains
unclear.
Chapter 3 demonstrated that a protein-polyphenol beverage (PPB) increases amino acid
availability and improved whole-body net balance versus carbohydrate placebo. In Chapter 4,
PPB accelerated recovery from muscle damage and stimulated rates of myofibrillar protein
synthesis thereafter. Thus, in the present study, it was hypothesised that the anabolic milieu
afforded by a post-exercise and pre-sleep PPB intervention would accelerate recovery from
any muscle damage and increase rates of MyoPS, thereby accelerating gains in strength and
muscle function over both 10 and 30 sessions of RET versus isocaloric carbohydrate placebo.
Given that individual, intrinsic rather than extrinsic factors appear stronger determinants of the
hypertrophic response (Damas et al., 2019; Stokes et al., 2020), this study employed a unilateral
training model with measurements made concurrently in the untrained leg to reduce
heterogeneity in response to RET.

165
5.3
Methods
5.3.1
Participants
The data presented in this chapter are part of a larger investigation into the effect of PPB on
manipulating training adaptations, whereby quadriceps muscle cross sectional area was chosen
as the primary outcome measure. An a prioi power calculation was performed based on
previously published work, where daily protein ingestion increased cross sectional area versus
placebo over 12 weeks of RET with an effect size of 0.91 (Snijders et al., 2015). Assuming
80% power and α = 0.05, 21 participants per group were calculated as required to observe this
effect.
Due to time constraints, thirty-two healthy, recreationally active male and female participants
volunteered to take part (16 male, 16 female; age: 24 ± 1 y; BMI: 23.0 ± 0.6 kg·m-2). Exclusion
criteria were: (1) diagnosed metabolic or cardiovascular impairment; (2) self-reported habitual
protein intake < 0.8 or > 1.6 g·kg-1·d-1; (3) musculoskeletal injury that may impair exercise
performance; (4) engagement in systematic resistance (> 2 times per week) or endurance
training (> 6 h per week) within six months of participation; (5) use of anti-inflammatory
medicines or nutritional supplements.
All individuals provided written consent at least 24 h after receiving verbal and written
explanation of the experimental procedures. This study was approved by the University of
Exeter’s Sport and Health Sciences Research Ethics Committee (Ref. No. 171206/B/09) and
registered with ClinicalTrials.gov (NCT03918395).

166
Figure 5.1. Graphical representation of the experimental protocol. 30 sessions of unilateral
resistance-type exercise training were performed with daily consumption of a post-exercise and
pre-bed protein-polyphenol intervention (PPB; n=15) or carbohydrate placebo (PLA; n=14).
Muscle strength and function were assessed bilaterally pre- and post-training, as well as every
3 training sessions during. Habitual dietary intake was recorded pre-, during, and post-training.
Bilateral muscle biopsies were obtained in the rested state pre- and post-training. A 48 h acute
measurement period began after the first training session with subsequent biopsies collected at
the end of this period.
5.3.2
General Study Design
Following enrolment, participants were randomly assigned using a double-blind, placebo-
controlled, parallel-group design to consume either daily post-exercise and pre-bed protein-
polyphenol beverages (PPB; n = 15) or daily post-exercise and pre-bed placebo beverages
(PLA; n = 14). Participant characteristics by group are shown in Table 5.1. Before the RET
program commenced, dietary intake records were collected and measurements of muscle
strength and function were obtained, alongside anthropometric measures of height and weight.

167
Table 5.1. Subject characteristics.
PLA
PPB
(n = 14)
(n = 15)
Sex (male:female)
7:7
7:8
Age (y)
25 ± 2
24 ± 1
Body mass (kg)
67.6 ± 2.5
65.5 ± 3.5
Height (cm)
168 ± 3
170 ± 3
BMI (kg·m-2)
23.9 ± 1.0
22.3 ± 0.7
Baseline strength (n∙m)
U: 185 ± 10
U: 211 ± 21
T: 184 ± 13
T: 204 ± 21
Baseline function (J)
U: 2172 ± 180
U: 2413 ± 216
T: 2204 ± 173
T: 2418 ± 232
Values represent mean ± SEM. PLA, maltodextrin placebo group; PPB, post-exercise and pre-
bed protein-polyphenol group; BMI, body mass index; U, untrained leg; T; trained leg.
Between-group comparisons P > 0.05.
This was repeated at regular intervals during the RET program as well as post-training (see
Figure 5.1 for a schematic overview). Muscle biopsy and venous blood samples were collected
pre- and post-training from a subset of participants (PLA: n = 10; PPB: n = 11). All strength
and function assessments as well as the RET program were performed on an isokinetic
dynamometer (Biodex System 3, Biodex Medical Systems, Inc., Shirley, NY, USA). One leg
was randomly allocated to undergo RET (T), with leg dominance counter-balanced within each
group, whilst the contralateral limb was assigned as the untrained, control (U). Prior data
collection, two familiarisation visits were performed to familiarise the participant with all
testing procedures described herein. Individual settings for the isokinetic dynamometer

168
(Biodex System 3, Biodex Medical Systems, Inc., Shirley, NY, USA) were determined on these
visits.
5.3.3
Muscle strength and function assessment
Participants visited the laboratory for pre-training measures of muscle strength and function,
performed in the fasted state and after abstaining from strenuous physical activity, alcohol and
anti-inflammatory or analgesic medication for 48 h and caffeine for 24 h.
Muscle strength was assessed by maximal isometric voluntary contraction of the knee extensor
muscles, as described in Chapter 2. After a task-specific warm-up consisting of 3 s isometric
contractions at 50% (x2), 75% (x1), and 90% (x1) of perceived maximal effort, participants
performed 3 x 3 s maximal isometric voluntary contractions at 75° knee flexion (full extension
corresponding to 0°). Participants received verbal encouragement and were instructed to push
as hard as possible for each of the contractions, which were separated by 60 s rest. Strength
was determined as the peak torque recorded over the 3 trials.
For the assessment of muscle function, participants performed 30 maximal isokinetic
contractions following a warm-up set of 5 submaximal contractions, using the isokinetic
dynamometer. Knee joint range of motion was set at 80° equidistant to full flexion and full
extension, as previously described in Chapter 2. Isokinetic function was calculated as the area
under the torque-time graph over the first 30 maximal repetitions in each leg.
All measurements were carried out in both T and U legs and repeated as described above post-
training. Additional bilateral measures of muscle strength and function were made 2 d after
every 3 training sessions to provide novel resolution on the time-course of training adaptations.

169
5.3.4
Acute testing period
Participants were instructed to avoid strenuous physical activity, alcohol and anti-inflammatory
or analgesic medication for 48 h prior to and throughout a 48 h acute testing period, which
began on the morning of the first training session (Figure 5.1). Following a > 10 h overnight
fast, participants arrived in the laboratory and muscle soreness was assessed via VAS, as
described in Chapter 2. A muscle biopsy was then collected from each leg, before commencing
the first supervised training session. After completion, participants consumed their post-
exercise beverage, as described below. These procedures were repeated 48 h later, on the
morning of the second training session, marking the end of the acute testing period. Participants
received full dietary control over this time.
5.3.5
Resistance-type exercise training program
Thirty sessions of supervised resistance-type exercise training were completed in total, with
sessions performed roughly 3 times·wk-1 separated by 2 ± 0 days. Each training session
consisted of 5 sets of 30 maximal isokinetic knee extensor contractions alternating between
concentric and eccentric contraction modalities (3 sets of concentric contractions and 2 sets of
eccentric contractions per session), which would be expected to induce significant hypertrophy
of the m. vastus lateralis (Franchi et al., 2018) and mimic a conventional resistance-type muscle
contraction involving both a concentric and eccentric contraction phase. Verbal encouragement
was provided throughout each set, and each set was separated by 120 s passive rest. Mean
duration for the RET program was 73 ± 2 and 73 ± 3 days for PLA and PPB groups,
respectively, with no differences between groups.
5.3.6
Nutritional intervention

170
Nutritional intervention began immediately after training session 1 and continued throughout
the RET program until the completion of the full study protocol. A post-exercise beverage was
provided to participants after completing each training session. Beverages were made up from
sachets containing either a commercially available post-exercise supplement (Beachbody
Performance Recover, Beachbody LLC, Santa Monica, CA, USA), providing 20 g total protein
(from a blend of whey, pea and casein), 10 g total carbohydrate and 650 mg pomegranate
extract (211 mg polyphenols; full composition shown in Appendix 2) for participants in PPB
treatment, or a taste- and colour-matched isocaloric, maltodextrin placebo for participants in
PLA, added to 225 mL of water. Afterwards, an additional 50 mL was added to the bottles and
given to the participants to ensure that all the contents were consumed.
Participants were provided with additional sachets to consume at home upon waking on non-
training days. Additionally, participants were provided with a pre-bed beverage to consume
within 30 minutes of going to bed each night. The pre-bed PPB beverage contained 18 g of
protein from micellar casein and 480 mg of tart cherry extract, or a taste- and colour-matched
isocaloric, maltodextrin beverage for participants in PLA. All drinks were well tolerated and
no adverse effects were reported during or after the experimental period. Adherence to the
nutritional intervention was assessed using a diary to record the time of consumption.
Adherence was 98 ± 1% in PLA and 99 ± 0% in PPB, with no differences between groups.
5.3.7
Dietary control and habitual dietary intake
Dietary control was employed for 48 h between training sessions 1 and 2 (acute testing period).
The full methodology is described in Chapter 2. Briefly, participants’ energy requirements
were calculated as the basal metabolic rate (estimated via the Henry equations) (Henry, 2005),
multiplied by an activity factor of 1.6 in order to maintain energy balance, as evidenced

171
previously (Chapter 4). Dietary protein provided by the controlled diet was clamped at 1.2 g·kg
body mass-1. No other energy-containing food or beverages were permitted over this time,
whereas water and non-caloric drinks were allowed ad libitum. Compliance with the nutritional
intervention was assessed via dietary records, returned food containers and daily
communication with the participants.
Before and after the RET program, participants were instructed to record a three-day, weighted,
habitual food diary, to include two weekdays and one weekend day. Further two-day habitual
food diaries were completed every six training sessions (approximately every two weeks) to
track habitual dietary intake throughout training. Habitual energy and macronutrient intakes
were calculated from these food diaries using online licensed software (Nutritics, Swords,
Dublin, Ireland).
5.3.8
Deuterated water dosing protocol
The full deuterated water dosing protocol is detailed in Chapter 2. Forty-eight hours before the
first training period, participants visited the laboratory to commence the dosing protocol. This
consisted of one loading day to enrich the body water pool to ~0.6%, followed thereafter by
three maintenance days.
5.3.9
Blood and muscle sampling
Blood and muscle samples were collected as described in Chapter 2. Briefly, fasted venous
blood samples were collected immediately prior to the deuterated water dosing protocol, and
immediately prior to each muscle biopsy. Samples were collected from the antecubital vein via
venepuncture technique into lithium heparin containers, which were immediately centrifuged

172
at 2850 x g for 10 min at 4°C. Plasma was aliquoted, frozen at -20°C and then transferred to
storage at -80°C for further analysis.
Muscle biopsies were obtained under local anaesthesia (2% lidocaine) from the mid-section of
the m. vastus lateralis by the Bergström needle technique modified for suction (Tarnopolsky
et al., 2011). All samples were rapidly dissected of visible fat and connective tissue, frozen in
liquid-nitrogen-cooled isopentane and stored at -80°C until subsequent analysis.
5.3.10
Plasma and muscle enrichment
Plasma hydrogen isotope ratios (2H/1H) were determined by injecting samples into a high-
temperature conversion elemental analyser (TCEA Flash 2000, ThermoFisher Scientific,
Waltham, MA, USA) coupled to an isotope ratio mass spectrometer (IRMS; Delta V,
ThermoFisher Scientific). Samples were run in triplicate. Raw isotope ratio values were
normalised to in-house reference materials calibrated to Vienna Standard Mean Ocean Water
(VSMOW).
The enrichment of [2H]-alanine in the myofibrillar fraction of skeletal muscle tissue samples
was determined as described in Chapter 2. Briefly, myofibrillar protein fractions were isolated
from ~50 mg wet weight muscle tissue. Tissue was homogenised and centrifuged, then
separated from the sarcoplasmic supernatant. The resultant pellet was solubilised in 0.3 M
NaOH and separated from the insoluble collagen fraction by centrifugation. Myofibrillar
proteins were precipitated with the addition of 1 M perchloric acid, washed twice in 70%
ethanol, and hydrolysed in 6 M HCl at 110°C for 24 h. Amino acids were purified using cation
exchange resin columns (100 – 200 mesh; H+ form; Dowex 50WX8; Sigma-Aldrich Company
Ltd.) and dried under vacuum before storage at -20°C.

173
Purified amino acids were derivatised to their tert-butyl-dimethylsilyl (TBDMS) esters
(Molnár-Perl & Katona, 2000) and injected into a Delta V Advantage IRMS (ThermoFisher
Scientific) fitted with a Trace 1310 gas chromatograph. Before pyrolysis and entry into the
IRMS, the peaks were separated on a 30m × 0.25mm ID × 0.25μm film DB-5 capillary column
(Agilent Technologies, Santa Clara, CA, USA; temperature program: 110°C for 1 min;
10°C∙min-1 ramp to 180°C; 5°C∙min-1 ramp to 220°C; 20°C∙min-1 ramp to 300°C; hold for 2
min). The enrichment of tracer was measured by monitoring ion masses 2 and 3 to determine
the 2H/1H ratios of myofibrillar protein-bound [2H]-alanine. A series of known standards were
applied to assess the linearity of the mass spectrometer.
5.3.11
Immunohistochemistry
Muscle biopsy samples collected prior to training session 1 and at the end of the RET program
were embedded in optimal cutting temperature compound to align fibres perpendicular to the
horizontal surface. Microtome-cryostat sections (7 μm thick) were obtained at −22°C and
mounted on to glass slides. Slides were subsequently defrosted to room temperature and fixed
in 4% paraformaldehyde in phosphate-buffered saline (PBS) for 15 min. After washing in PBS,
a PBS-based blocking solution (5% foetal bovine serum, 2% bovine serum albumin, 2% goat
serum, 0.2% Triton X-100 and 0.1% sodium azide) was applied for 60 min followed by
overnight incubation at 4°C with primary antibody against Pax7 (1:40 in PBS; Developmental
Studies Hybridoma Bank, Iowa City, IA, USA; RRID: AB_528428). The following morning,
slides were washed in PBS and incubated for 2 h with primary antibody against laminin (1:100;
Developmental Studies Hybridoma Bank; RRID: AB_2134060) and myosin heavy chain type
I (1:100; Developmental Studies Hybridoma Bank; RRID: AB_528384) in PBS. After
washing, slides were incubated for 2 h in PBS containing secondary antibodies for Pax7 (1:50;

174
Alexa Fluor 488, Invitrogen, Paisley, UK; RRID: AB_2535764), laminin (1:250; Alexa Fluor
568, Invitrogen; RRID: AB_2535773), and myosin heavy chain type I (1:100; Alexa Fluor 647,
Abcam PLC, Cambridge, UK), with 42mM DAPI. After a final washing step, slides were
mounted with cover glass with Mowiol (Sigma-Aldrich Company Ltd.).
All images were captured digitally (LAS X software; Leica Microsystems GmbH, Wetzlar,
Germany) using a Leica DMi8 S widefield fluorescence microscope (Leica Microsystems
GmbH) coupled to a Hamamatsu C11440-22C camera (Hamamatsu Photonics, Shizuoka,
Japan) at x20 magnification. Epifluorescence signal was recorded by using excitation filters
for DAPI (400 nm), laminin (Texas Red, 540–580 nm), PAX7 (FITC, 465–495 nm), and MHC-
I (Y5, 620-650 nm). Image processing and quantitative analysis were conducted by using the
open-source Fiji software platform (Schindelin et al., 2012) with the MuscleJ plug-in (Mayeuf-
Louchart et al., 2018), to quantify satellite cell number, fibre type and the mean fibre cross-
sectional area (fCSA). Following quantification, regions of interest were manually verified,
and any misidentified fibres were removed from the subsequent analysis. Following this
correction, 329 ± 31 fibres were analysed per section. As a measure of fibre circularity, form
factors were calculated by using the following formula:
4𝜋×𝐶𝑆𝐴
𝑝𝑒𝑟𝑖𝑚𝑒𝑡𝑒𝑟
2
(5.1)
Fibres were not analysed if the form factor was below 0.4.
5.3.12
Calculations

175
𝑖
Myofibrillar protein fractional synthesis rates (myoFSR) were calculated based on the
incorporation of [2H]-alanine into myofibrillar protein and mean plasma deuterium enrichment
between muscle biopsy time points corrected by a factor of 3.7, based on the deuterium
labelling of alanine. MyoFSR was calculated using the following precursor-product equation:
𝑚𝑦𝑜FSR (%·d-1) = ( Em2 – Em1 ) × 100 (5.2)
3.7 × Ep × t
Where Em1 and Em2 are the myofibrillar protein-bound alanine enrichments expressed as mole
per cent excess (MPE), Ep represents mean precursor enrichment between given time points
and t is the time between the corresponding biopsies for which FSR is calculated, expressed as
days (d).
To calculate the rate of training volume improvement over early (sessions 1-10), middle
(sessions 11-20) and late (sessions 21-30) sessions, expressed as a percentage of starting
volume, the following formula was used:
∑
𝑛
(𝖶
𝑖+1
−𝖶
𝑖
)
𝖶
1
×(𝑛+1−𝑖)
× 100 (5.3)
Where W is work done in a given session; and for the early, middle and late training sessions,
n is either 9, 19 or 29 and i is either 1, 11 or 21, respectively.
5.3.13
Statistical analysis

176
Baseline characteristics between groups were investigated using a student’s independent t-test.
A two-way mixed model ANOVA was used to identify differences between pre-training
habitual diet versus controlled diet (diet and group factors), habitual diet throughout training
(time and group factors), total work performed throughout training (time and group factors),
muscle strength and function (time and group factors), changes in the fCSA and fibre type
proportion (time and group factors), the satellite cell content per muscle fibre (time and group
factors). A three-way ANOVA was used to identify improvements in work performed by
contraction type, expressed as the percentage of work performed in session 1 (time, group and
contraction type factors). Interaction effects were followed up using two-way mixed model
ANOVAs. Correlation analyses were performed using Pearson’s product moment correlation
between training adaptations and MyoPS for participants where full sets of data were obtained.
Correlation coefficients |r| < 0.2 were considered small; 0.2 < |r| < 0.7, moderate; and |r| > 0.7,
high. Significance level was set as P < 0.05, whereas trends were noted if 0.05 < P < 0.10.
5.4
Results
Participant characteristics for each treatment group are shown in Table 5.1. Three subjects did
not complete the full experimental protocol; two due to personal circumstances and one due to
time commitments, thus data from 29 participants were included in the final dataset (PLA: n =
14; PPB: n = 15). Upon completion of the study, participants were asked whether they could
identify the intervention they had been assigned to; four participants in PLA and eight
participants in PPB had correctly identified their group, whereas the remaining eight
participants in PLA and five participants in PPB either did not know or guessed incorrectly.
Skeletal muscle biopsy samples were obtained for n = 10 in PLA and n = 11 in PPB. Over the
RET program, body weight and BMI did not change.

177
Table 5.2. Habitual diet pre, during and post 30 sessions of resistance-type exercise training in
a group allocated to consume a daily post-exercise and pre-bed maltodextrin placebo (PLA)
nutritional intervention
PLA
Pre
Session 7
Session 13
Session 19
Session 25
Post
Energy (MJ·d-1)
9.7 ± 8.7
9.8 ± 7.7
9.5 ± 8.2
9.1 ± 4.8
9.7 ± 6.3
9.1 ± 5.8
Protein (g·kg
bm-1·d-1)
1.5 ± 0.2
1.5 ± 0.3
1.2 ± 0.1
1.2 ± 0.1
1.4 ± 0.1
1.3 ± 0.1
Protein (g·d-1)
98 ± 12
97 ± 16
80 ± 9
83 ± 7
94 ± 7
85 ± 7
Carbohydrates
(g·d-1)
284 ± 24
273 ± 18
273 ± 27
272 ± 18
272 ± 21
266 ± 20
Fat (g·d-1)
84 ± 10
91 ± 9
87 ± 10
77 ± 4
92 ± 8
80 ± 6
Protein (En%)
17 ± 1
16 ± 2
14 ± 1
15 ± 1
16 ± 1
16 ± 1
Carbohydrates
50 ± 2
48 ± 2
48 ± 2
50 ± 1
47 ± 2
49 ± 2
(En%)
Fat (En%)
32 ± 2
34 ± 2
34 ± 2
32 ± 1
35 ± 2
33 ± 1
Values represent mean ± SEM. A two-way ANOVA was used to detect differences over time
and compared to PPB (Table 5.3).

178
Table 5.3. Habitual diet pre, during and post 30 sessions of resistance-type exercise training in
a group allocated to consume a daily post-exercise and pre-bed protein-polyphenol (PPB)
nutritional intervention
PPB
Pre
Session 7
Session 13
Session 19
Session 25
Post
Energy (MJ·d-1)
9.3 ± 8
8.8 ± 7.7
8.8 ± 7.3
7.8 ± 5.7
8 ± 6.3
9.2 ± 5.6
Protein
1.8 ± 0.1
1.8 ± 0.1
1.7 ± 0.1
1.7 ± 0.1
1.7 ± 0.1
1.8 ± 0.1
(g·kg bm-1·d-1)
Protein (g·d-1)
115 ± 8
116 ± 9
106 ± 6
108 ± 7
107 ± 6
115 ± 8
Carbohydrates
(g·d-1)
247 ± 22
235 ± 19
233 ± 22
211 ± 15
219 ± 20
247 ± 15
Fat (g·d-1)
85 ± 11
76 ± 11
81 ± 8
65 ± 8
64 ± 7
82 ± 7
Protein (En%)
22 ± 1
23 ± 2
21 ± 1
24 ± 1
23 ± 1
21 ± 1
Carbohydrates
45 ± 2
45 ± 2
44 ± 2
46 ± 2
46 ± 2
45 ± 1
(En%)
Fat (En%)
33 ± 2
31 ± 2
34 ± 2
30 ± 2
30 ± 2
33 ± 1
Values represent mean ± SEM. A two-way ANOVA was used to detect differences over time
and compared to PLA (Table 5.2). Significant main effect of group for protein intake (g·kg bm-
1·d-1 , g·d-1, and En%, all P < 0.001).

179
5.4.1
Dietary intake
There were no group differences in self-reported, habitual diet assessed pre-training. Total
daily energy intake during the period of controlled diet (11.2 ± 0.5 and 10.1 ± 0.5 MJ·d-1 for
PLA and PPB, respectively) was significantly greater than habitually reported pre-training (8.7
± 0.9 and 8.3 ± 0.8 for PLA and PPB respectively; P < 0.001). Similarly, total daily
carbohydrate increased during the controlled diet, (PLA: 231 ± 24 to 351 ± 19 g·d-1; PPB: 232
± 22 to 290 ± 17 g·d-1; pre-training to controlled diet, respectively; time effect P < 0.001, time
x group interaction P = 0.051), whereas total daily fat intake was unchanged (83 ± 10 and 84
± 11 g·d-1 pre-training, to 96 ± 4 and 82 ± 6 g·d-1 during the controlled diet, for PLA and PPB,
respectively). During the controlled diet, daily protein intake increased only with PPB
intervention (PLA: 96 ± 12 to 84 ± 3 g·d-1; PPB: 77 ± 8 to 114 ± 4 g· d-1; pre-training to
controlled diet, respectively; group x time interaction P < 0.01). Expressed relative to body
weight, protein ingestion was significantly greater with PPB than PLA only during the
controlled diet (pre-training: 1.44 ± 0.19 versus 1.21 ± 0.12 g·kg BM·d-1; controlled diet: 1.25
± 0.03 versus 1.76 ± 0.04 g·kg BM·d-1; group x time interaction P < 0.01).
Analysis of dietary intake records collected throughout RET showed no change in total daily
energy, protein, carbohydrate or fat intake over time, expressed as both absolute values and
relative to body mass (Tables 5.2 and 5.3). Intervention with PPB increased total daily protein
intake (P < 0.001), protein intake relative to body mass (P < 0.001), and protein as a
contribution to daily energy intake (P < 0.001) relative to PLA.
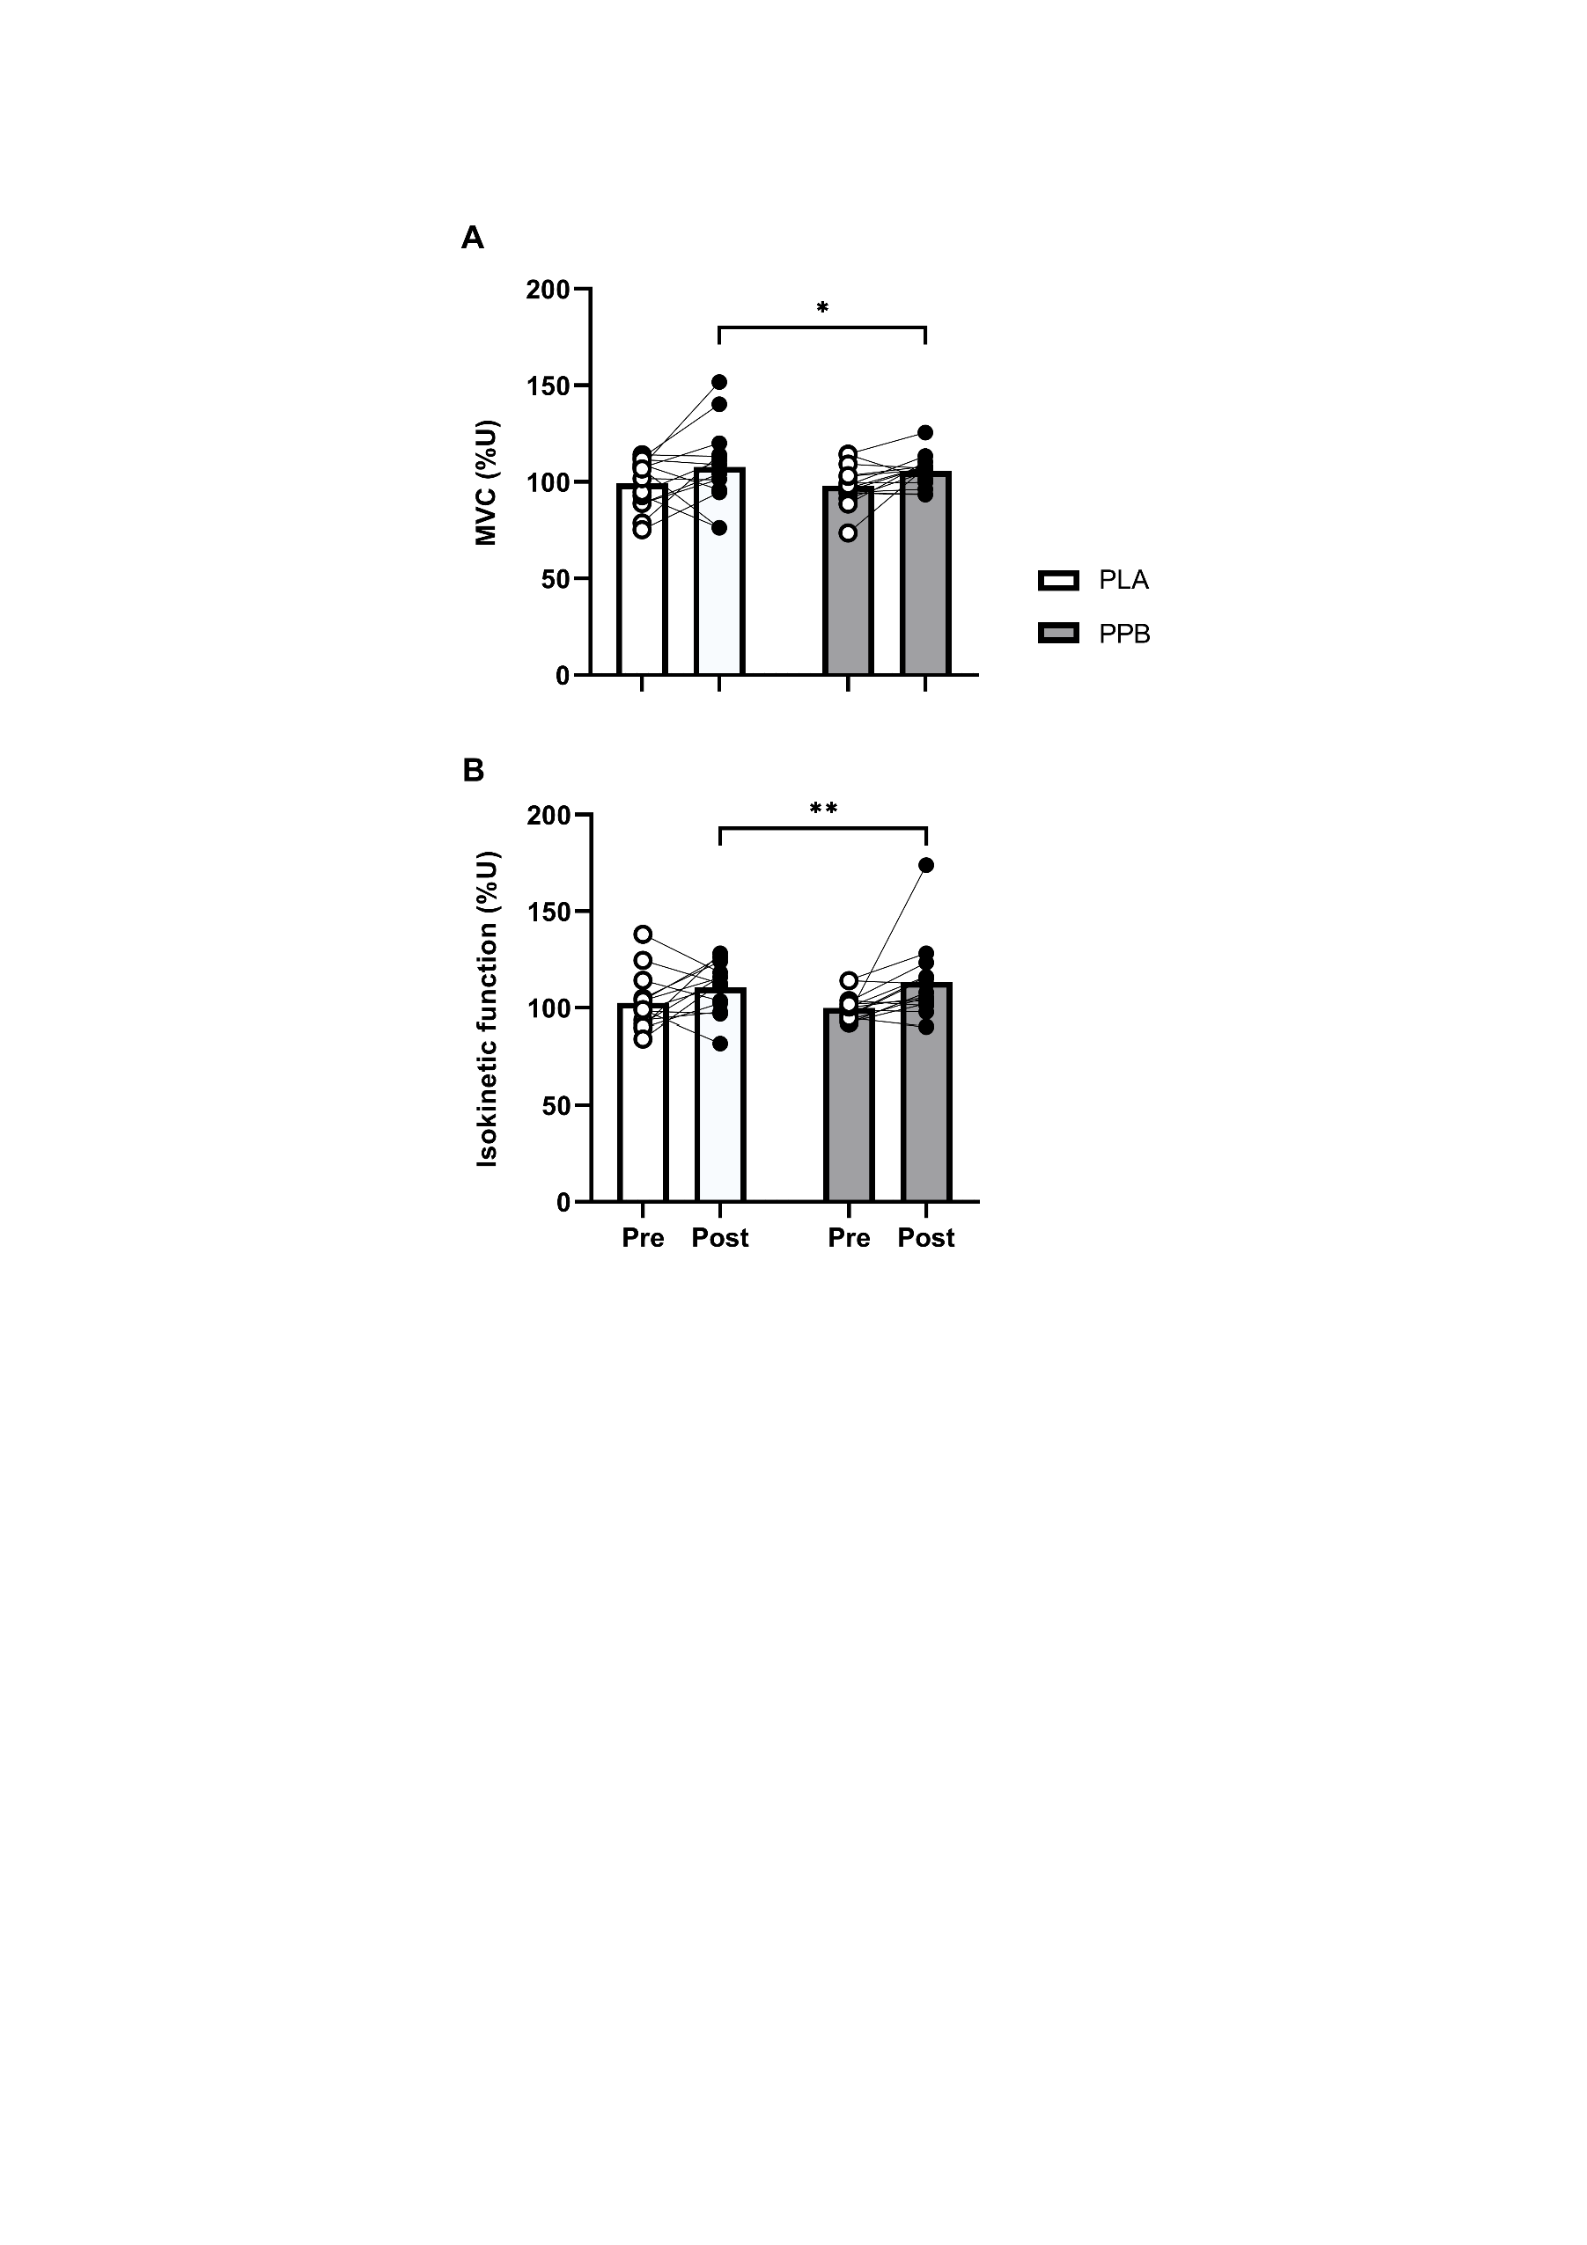
180
Figure 5.2. Knee extensor maximal voluntary contraction (MVC) strength (A) and function
(B) measured pre- and post- 30 sessions of unilateral resistance-type exercise, expressed
relative to the untrained leg (%U). A post-exercise and pre-bed protein-polyphenol (PPB; grey
bars) or maltodextrin placebo (PLA; white bars) nutritional intervention was provided daily.
Significant main effects of time denoted by *P < 0.05, **P < 0.01 significantly different to
pre-training.
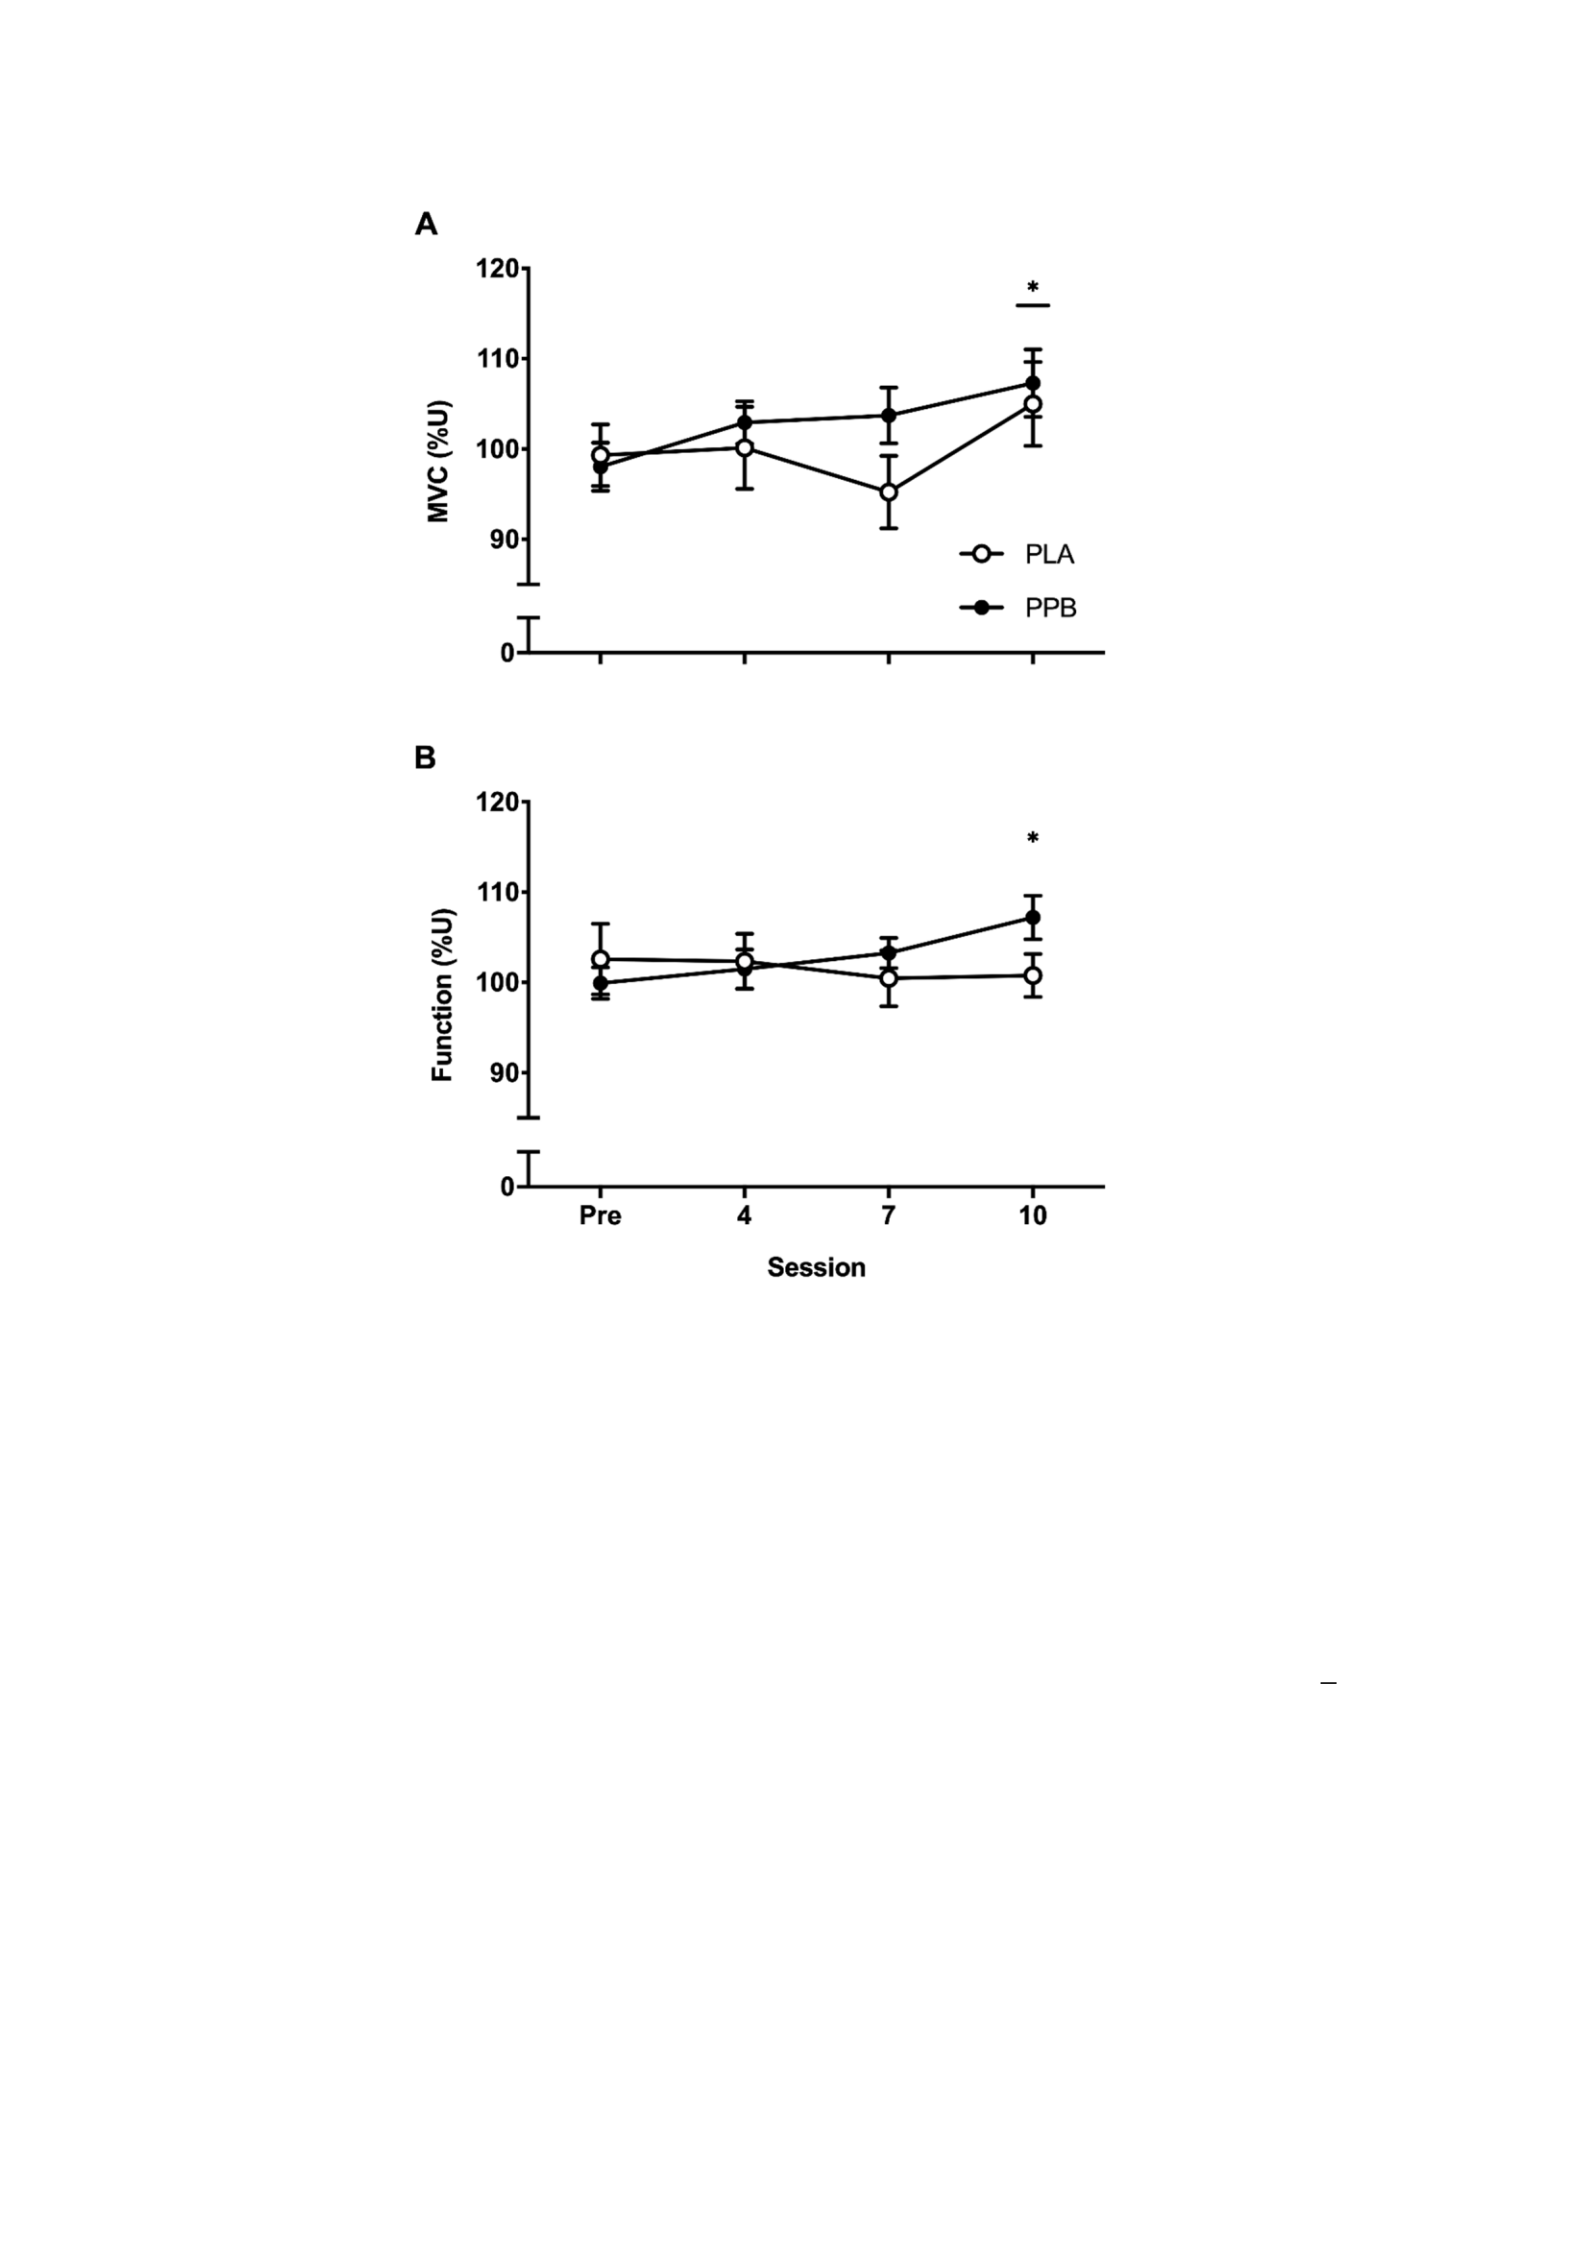
181
Figure 5.3. Early changes in knee extensor A: strength, defined as maximal voluntary isometric
contraction (MVC); and B: function; measured pre-training, and immediately before sessions
4, 7 and 10. A post-exercise and pre-bed protein-polyphenol (PPB; filled circles) or
maltodextrin placebo (PLA; open circles) nutritional intervention was consumed daily. Values
are expressed relative to the untrained leg (%U). A: Significant main effect of time (P < 0.05).
B: Significant time x group interaction (P < 0.05). Post hoc differences denoted by A: *P <
0.05 greater than pre; B: *P < 0.05 significantly greater in PPB only than pre.
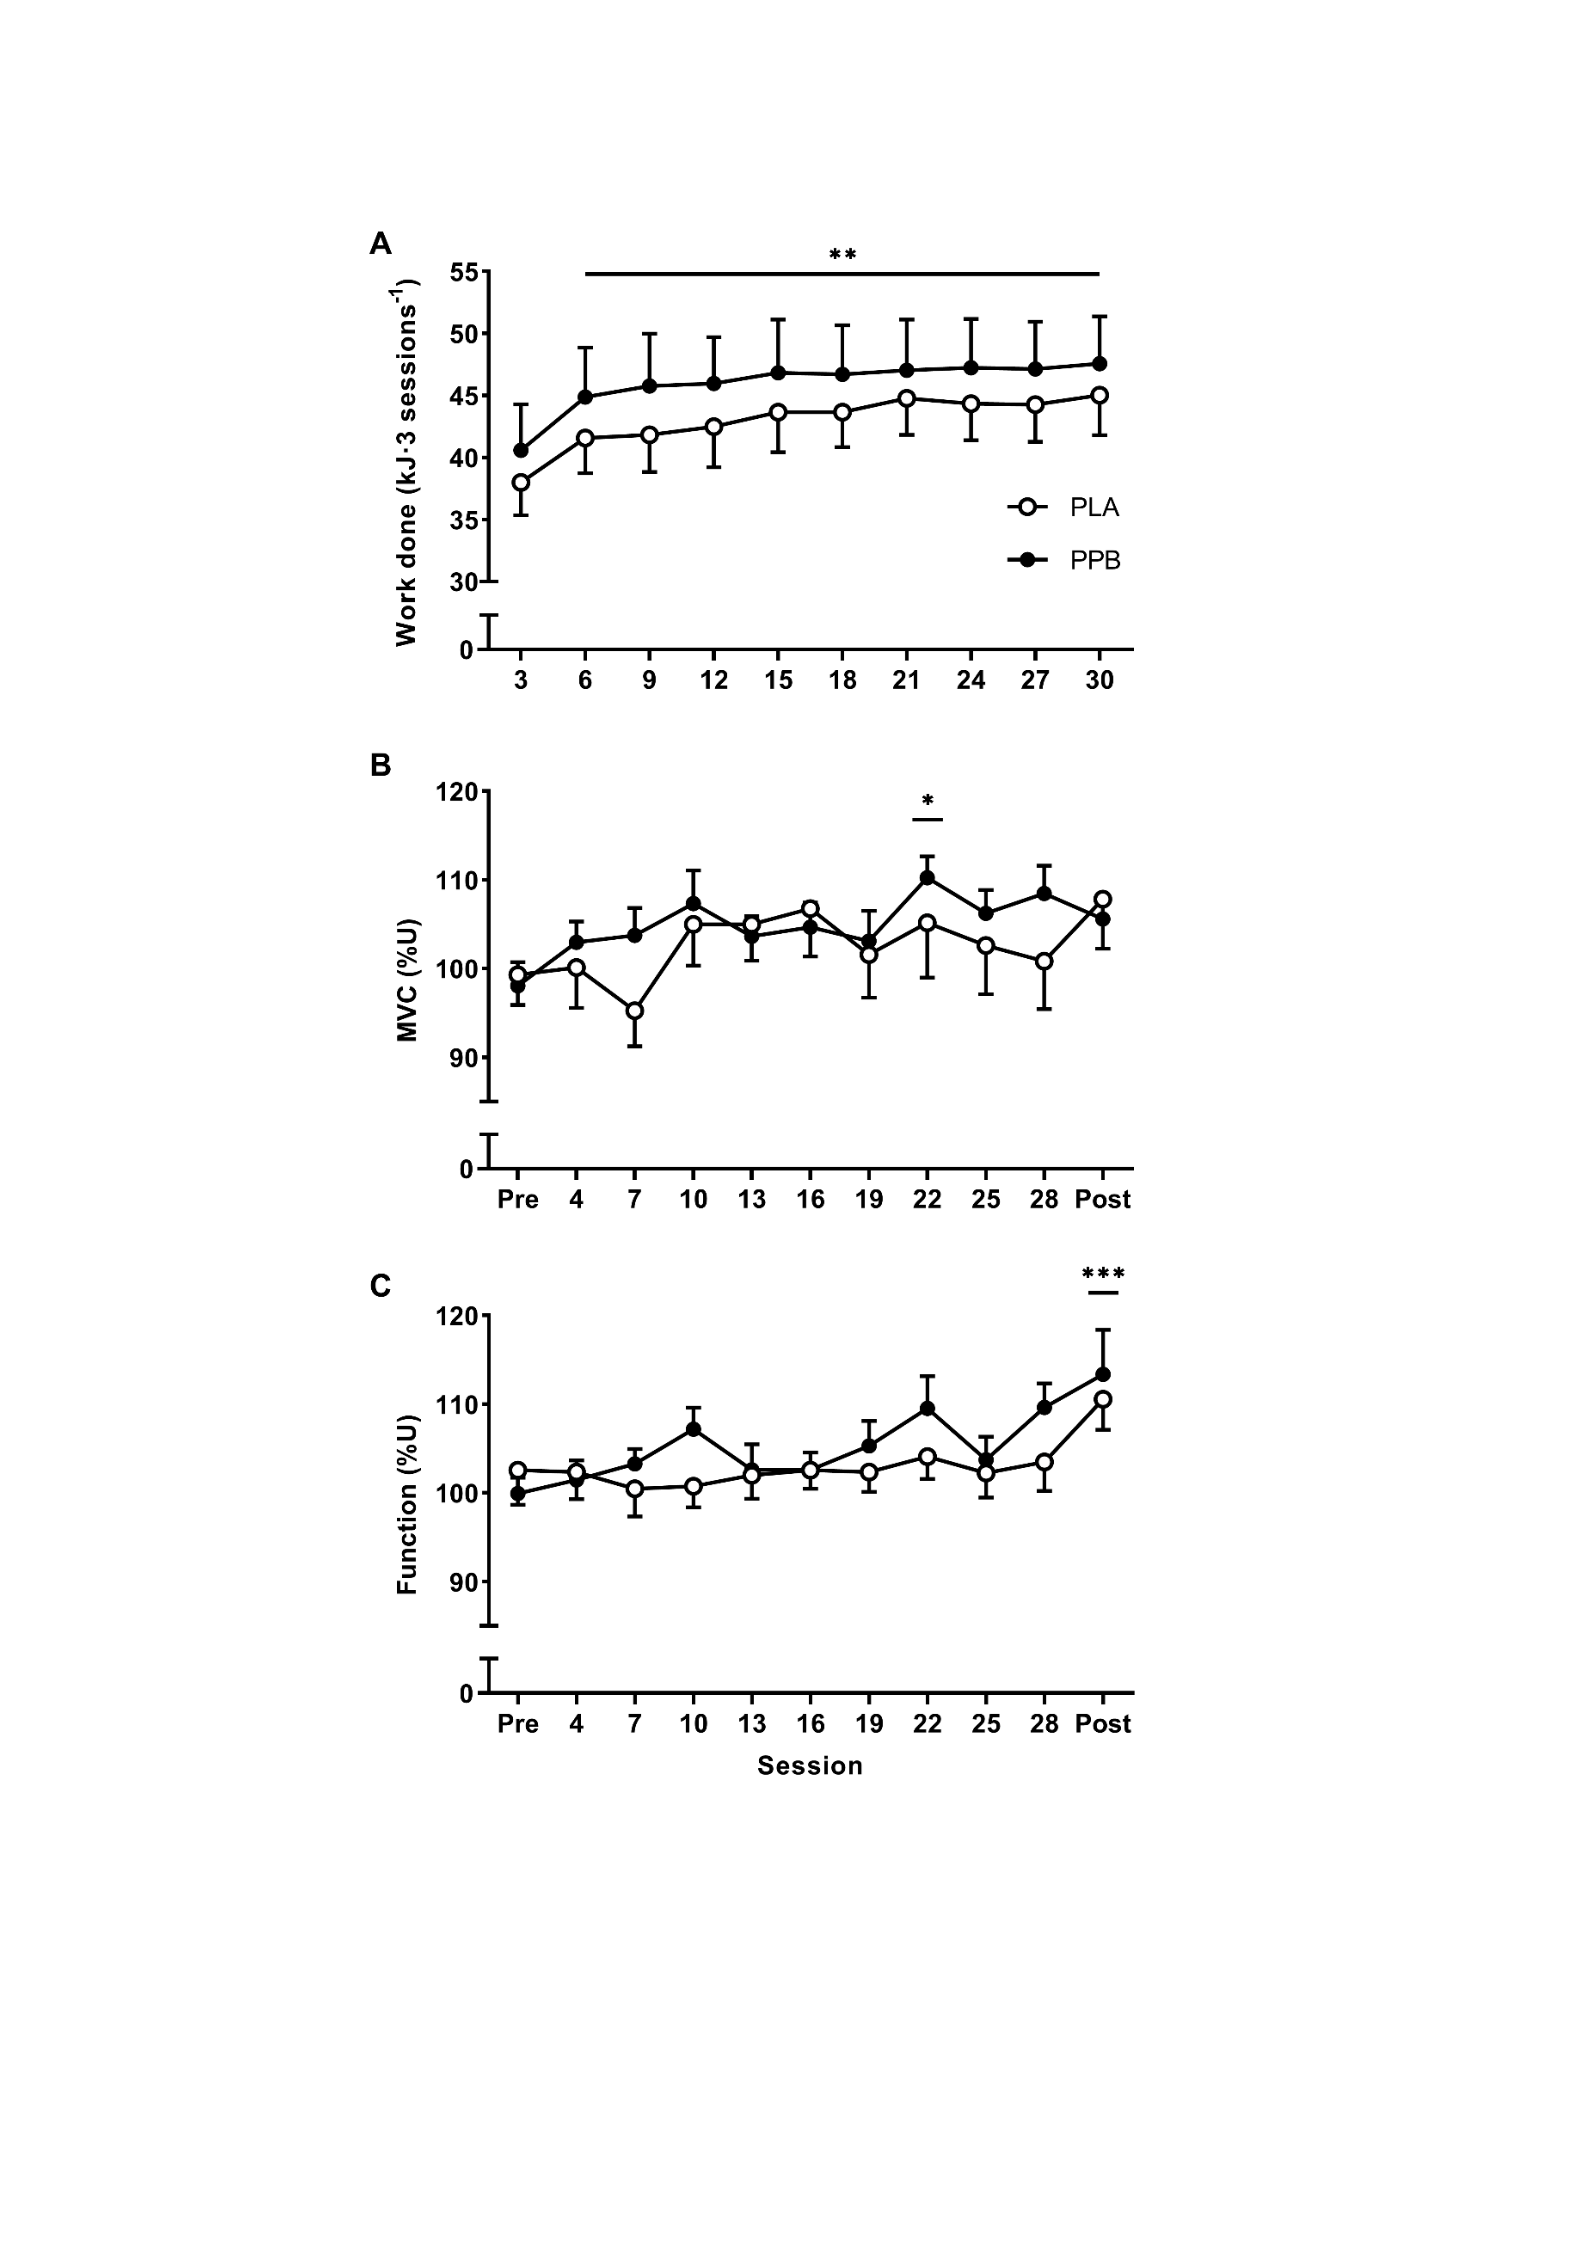
182

183
Figure 5.4. (Overleaf). Time-course of changes in A: total training volume measured as work
done over 3 training sessions; B: Muscle strength, defined as maximal voluntary isometric
contraction (MVC) expressed relative to the untrained leg (%U); and C: Muscle function,
defined as total work performed over 30 maximal, voluntary, isokinetic, concentric
contractions, expressed relative to the untrained leg (%U); over 30 sessions of unilateral
resistance-type exercise training. A post-exercise and pre-bed protein-polyphenol (PPB; filled
circles) or maltodextrin placebo (PLA; open circles) nutritional intervention was consumed
daily. A: Significant main effect of time (P < 0.001). B: Significant main effect of time (P <
0.01). C: Significant main effect of time (P < 0.001). Post hoc differences denoted by A: **P
< 0.01 greater than session 3; B: *P < 0.05 greater than pre; C: ***P < 0.001 greater than pre.
5.4.2
Muscle strength and function
Training session 10 marked the end of the early phase of training and was performed 3.0 ± 0.1
weeks after onset of RET. Muscle strength (Figure 5.3A) increased from pre-training to session
10 in PLA (99.3 ± 3.4 to 105.0 ± 4.7 %U, pre to session 10 respectively), and to a similar extent
in PPB (98.0 ± 2.7 to 107.2 ± 2.4 %U; pre to session 10 respectively; time effect P < 0.05). In
PLA, muscle function over the early phase of training was unaffected by RET (Figure 5.3B),
from 102.6 ± 3.9 %U pre-training to 100.8 ± 2.4 %U at session 10. However, PPB increased
function from 99.9 ± 1.8 %U to 107.2 ± 2.4 %U at session 10 (time x group interaction P <
0.05).
No differences were observed in baseline muscle strength or function, either between legs or
between groups (Table 5.1). Thirty sessions of RET significantly increased MVC strength from
99.3 ± 3.4 to 107.8 ± 5.6 %U pre- to post-training in PLA. PPB did not affect this gain,
increasing from 98.0 ± 2.7 to 105.6 ± 2.1 %U (time effect P < 0.05; Figure 5.2A). Muscle
function was increased by RET, from 102.6 ± 3.9 to 110.6 ± 3.4 %U pre- to post-training in

184
PLA (time effect P < 0.01; Figure 5.2B). A similar increase was observed in PPB (99.9 ± 1.8
to 113.5 ± 5.0 %U pre- to post-training), revealing no effect of nutritional intervention on
muscle function.
A separate analysis on the weekly assessments of muscle MVC revealed a significant increase
over time (P < 0.01; Figure 5.4B), with post hoc analysis identifying session 22 (PLA: 105.2 ±
6.2 %U; PPB: 110.2 ± 2.4 %U) as significantly greater than pre-training. Functional
assessments showed a significant increase over time, with only post-training function being
significantly greater than pre-training (P < 0.001; Figure 5.4C).
5.4.3
Training volume
The total work performed during each training session increased over time in both groups (P <
0.001; Figure 5.4A). In PLA, 29 ± 7% more work was performed in session 30 than in session
1 (Figure 5.4A). Intervention with PPB did not influence the volume of work performed at any
time point, with 25 ± 7% more work performed in session 30 than in session 1. Cumulative
work performed by session 4 (7.3 ± 0.3 d following initial training session) was unaffected by
PPB intervention (PLA: 52.9 ± 4.4 kJ; PPB: 54.4 ± 4.4 kJ). By session 10, PLA and PPB had
performed similar volumes of work (137.7 ± 11.5 kJ; 144.1 ± 11.7 kJ).
Total concentric work and total eccentric work increased over time but was modified by
contraction type (time x contraction type interaction P < 0.001). However, this was unaffected
by PPB intervention. By set 30, concentric work increased 18 ± 5% and 14 ± 6% for PLA and
PPB, respectively (post hoc versus set 1; P < 0.01). Eccentric work increased 39 ± 11% and 36
± 8% for PLA and PPB (post hoc versus set 1; P < 0.001), but this improvement was not
significantly different to that of concentric work at this time point. A greater volume of
eccentric work was performed from session 4 onwards relative to session 1, whereas a greater

185
volume of concentric work was consistently observed after session 20 (time x contraction type
interaction P < 0.001).
The rate of improvement in training volume (Figure 5.5A: Total; B: concentric; C: eccentric
volumes) was greatest over the early phase of training and decreased in middle and later phases
(time effect; total: P < 0.001; concentric; P < 0.05; eccentric; P < 0.001). PPB did not influence
the rate of improvement in training volume at any stage.
5.4.4
Muscle soreness
Baseline muscle soreness measured before the first training session was 4 ± 2 and 3 ± 1 mm in
PLA and PPB respectively. The onset of training significantly increased muscle soreness (P <
0.001), such that before session two, 48 h after the first training session, muscle soreness had
increased to 7 ± 2 and 9 ± 2 mm in PLA and PPB (P < 0.001), respectively. Before session
three, muscle soreness was significantly lower and had returned to baseline (2 ± 1 and 4 ± 1
mm in PLA and PPB, respectively; P < 0.001). Intervention with PPB did not affect muscle
soreness compared to PLA.
5.4.5
Fibre characteristics
Due to limited remaining tissue, fCSA was determined in n = 9 for both groups. A
representative image is shown in Figure 5.6. Expressed relative to the untrained leg (%U),
mean fCSA was 120.5 ± 7.4 and 109.5 ± 8.6 %U pre- and post-training in PLA. This change
was influenced by PPB, such that fCSA was 91.5 ± 6.1 and 111.8 ± 10.7 %U pre- and post-
training (time x group interaction P < 0.05).

186
Type I fibre size was unaffected by RET and by PPB intervention (Figure 5.7A). In PLA, mean
type II fibre size was 120.8 ± 8.2 %U pre-training and 105.0 ± 7.9 %U post-training. However,
PPB was 92.8 ± 6.2 %U pre-training and 108.4 ± 9.7 %U post-training (Figure 5.7B; time x
group interaction P < 0.05).
Pre-training, the proportion of fibres that were type II was similar between U and T legs (61 ±
3% and 55 ± 3%, respectively) in PLA. The proportion was similar in PPB (64 ± 2% and 61 ±
5% in U and T respectively). Post-training, the proportion of type II fibres was unchanged
(PLA: 58 ± 5% and 59 ± 5%; PPB: 57 ± 4% and 61 ± 3%; U and T, respectively; all
comparisons P > 0.05).
The number of satellite cells per fibre pre-training was 0.020 ± 0.007 and 0.027 ± 0.008
SC·fibre-1 in U and T legs in PLA. This was unaffected by training, at 0.034 ± 0.008 and 0.024
± 0.008 SC·fibre-1 in U and T, respectively. This response was similar to PPB, at 0.019 ± 0.006
and 0.014 ± 0.004 SC·fibre-1 in U and T legs pre-training, to 0.025 ± 0.006 and 0.028 ± 0.008
SC·fibre-1 in U and T legs post-training (all comparisons P > 0.05).
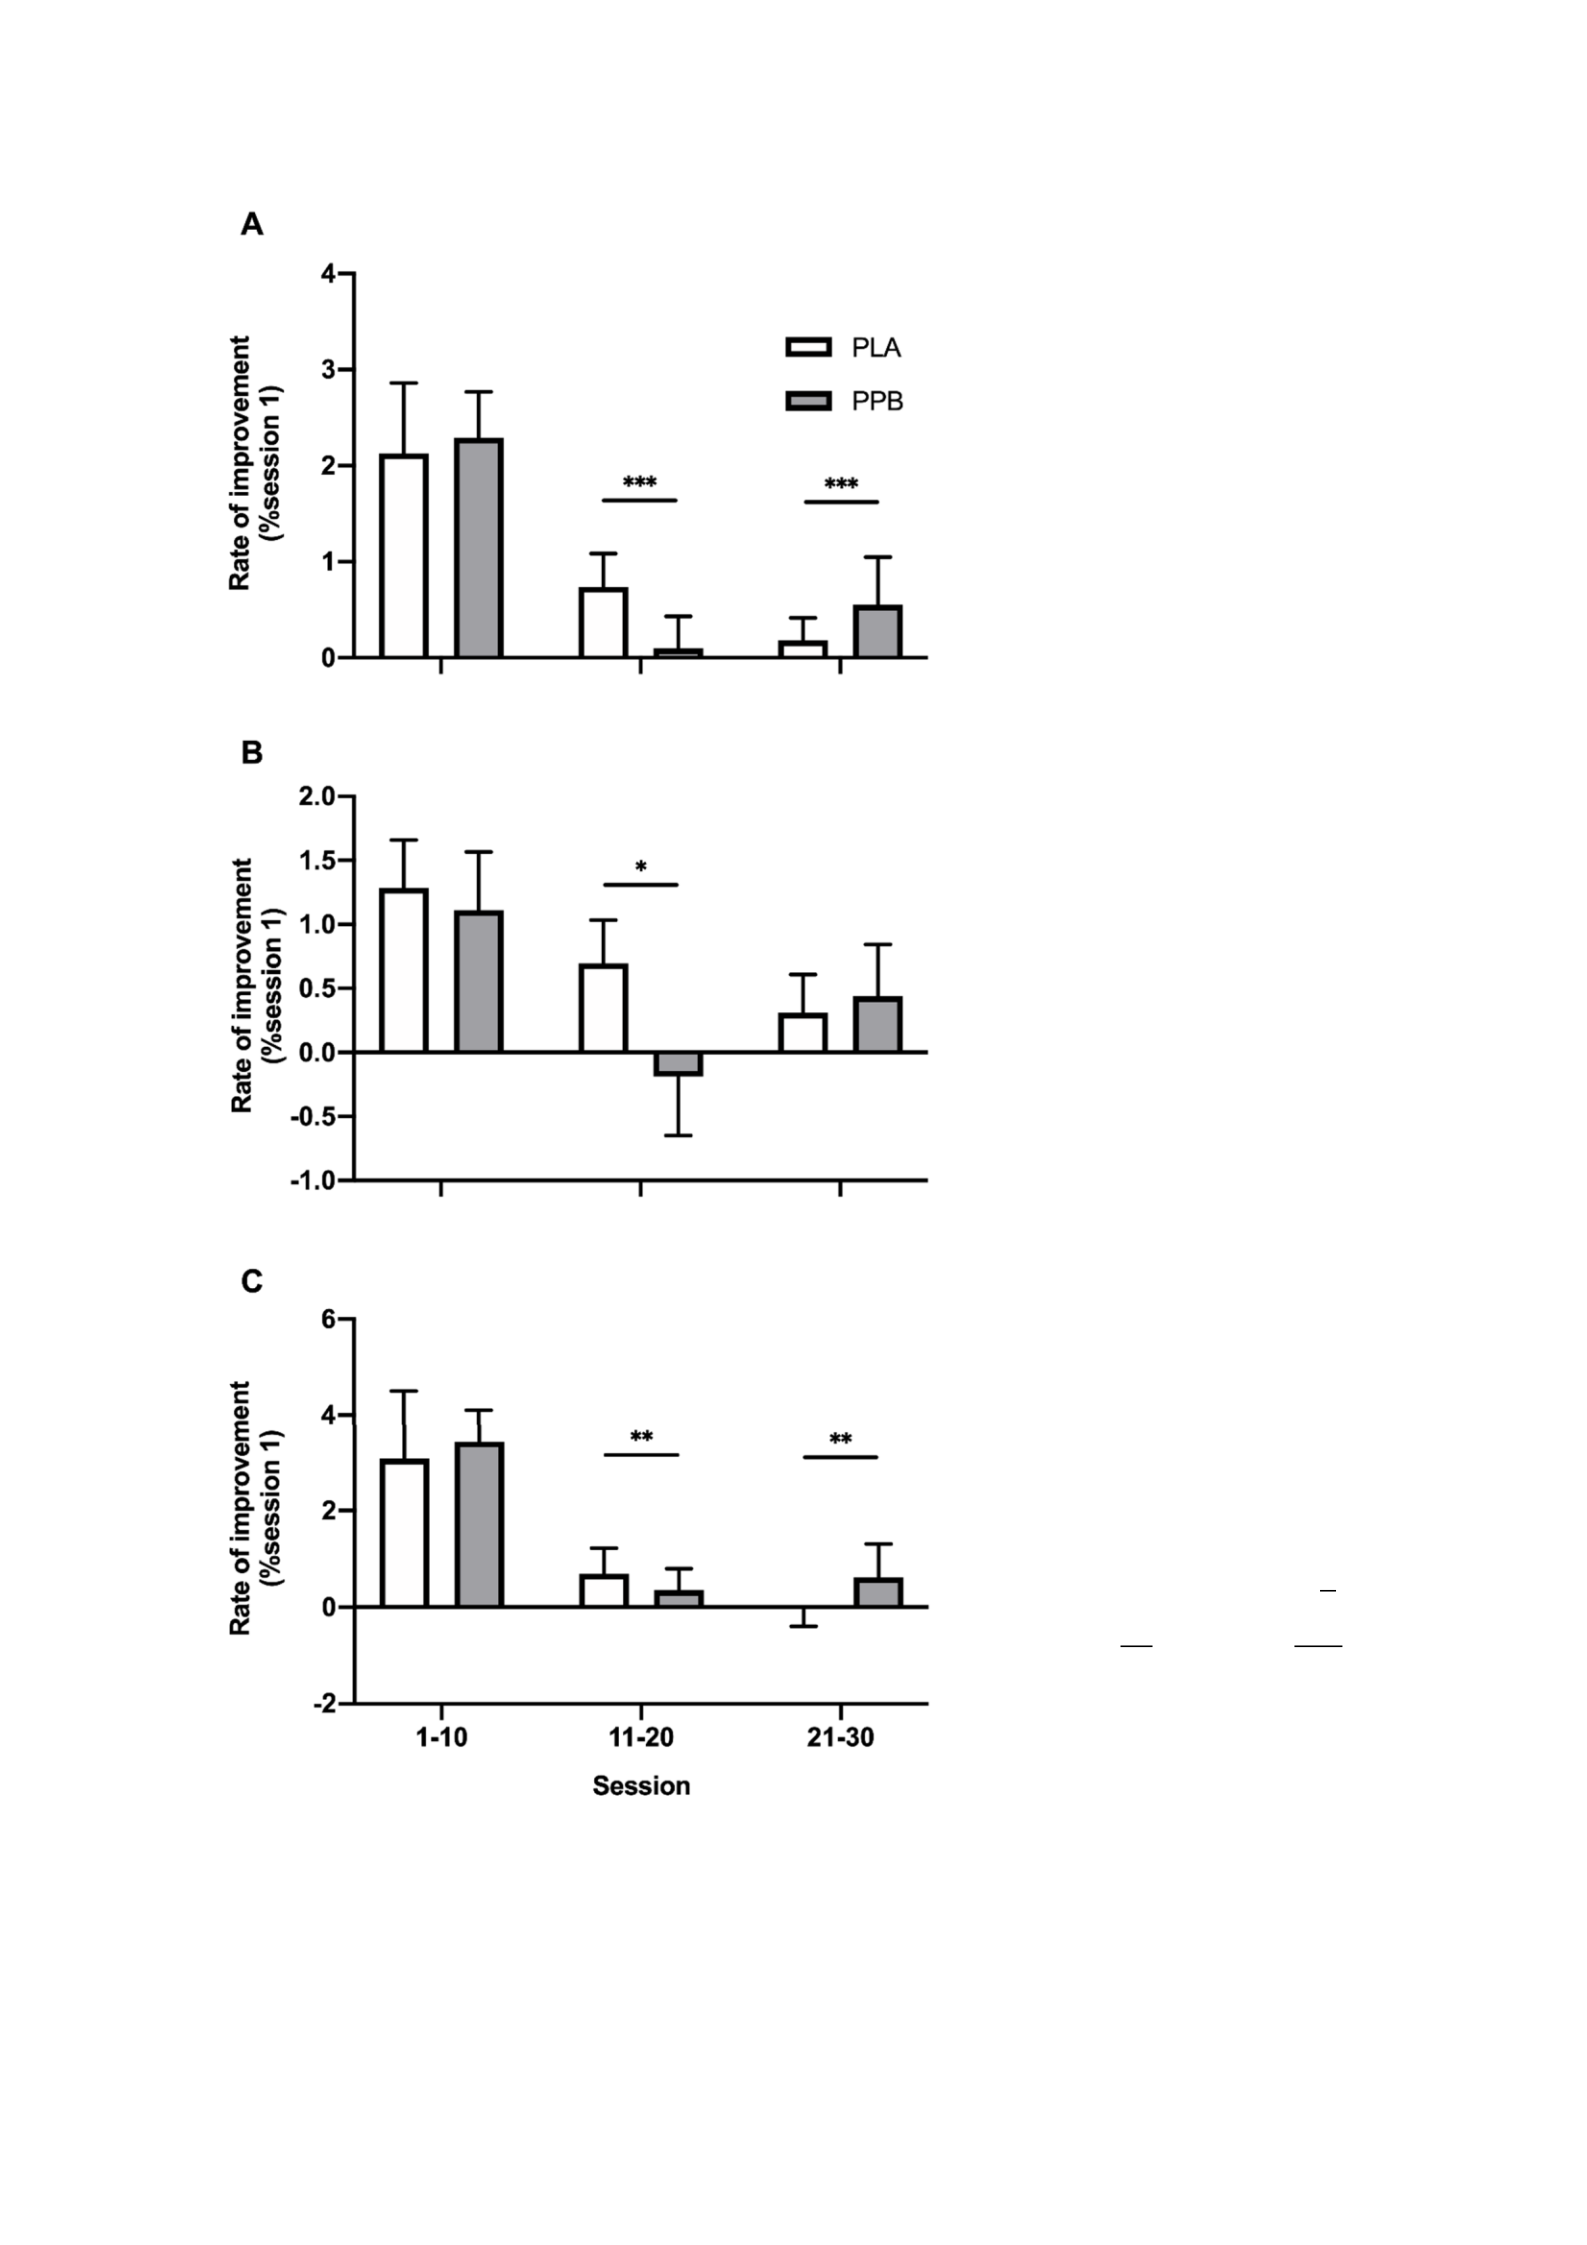
187
Figure 5.5. Mean rate of
improvement between
training sessions 1-10, 11-
20 and 21-30 for A: total
work performed; B: total
concentric work
performed; C: total
eccentric work performed;
expressed relative to work
performed in session 1. A
post-exercise and pre-bed
protein-polyphenol (PPB;
filled bars) or maltodextrin
placebo (PLA; open bars)
nutritional intervention was
consumed daily. A:
Significant main effect of
time (P < 0.001). B:
Significant main effect of
time (P < 0.05). C:
Significant main effect of
time (P < 0.001). Post hoc
difference within time
effect denoted by *P <
0.05, **P < 0.01, ***P <
0.001 decrease from
session 1-10.
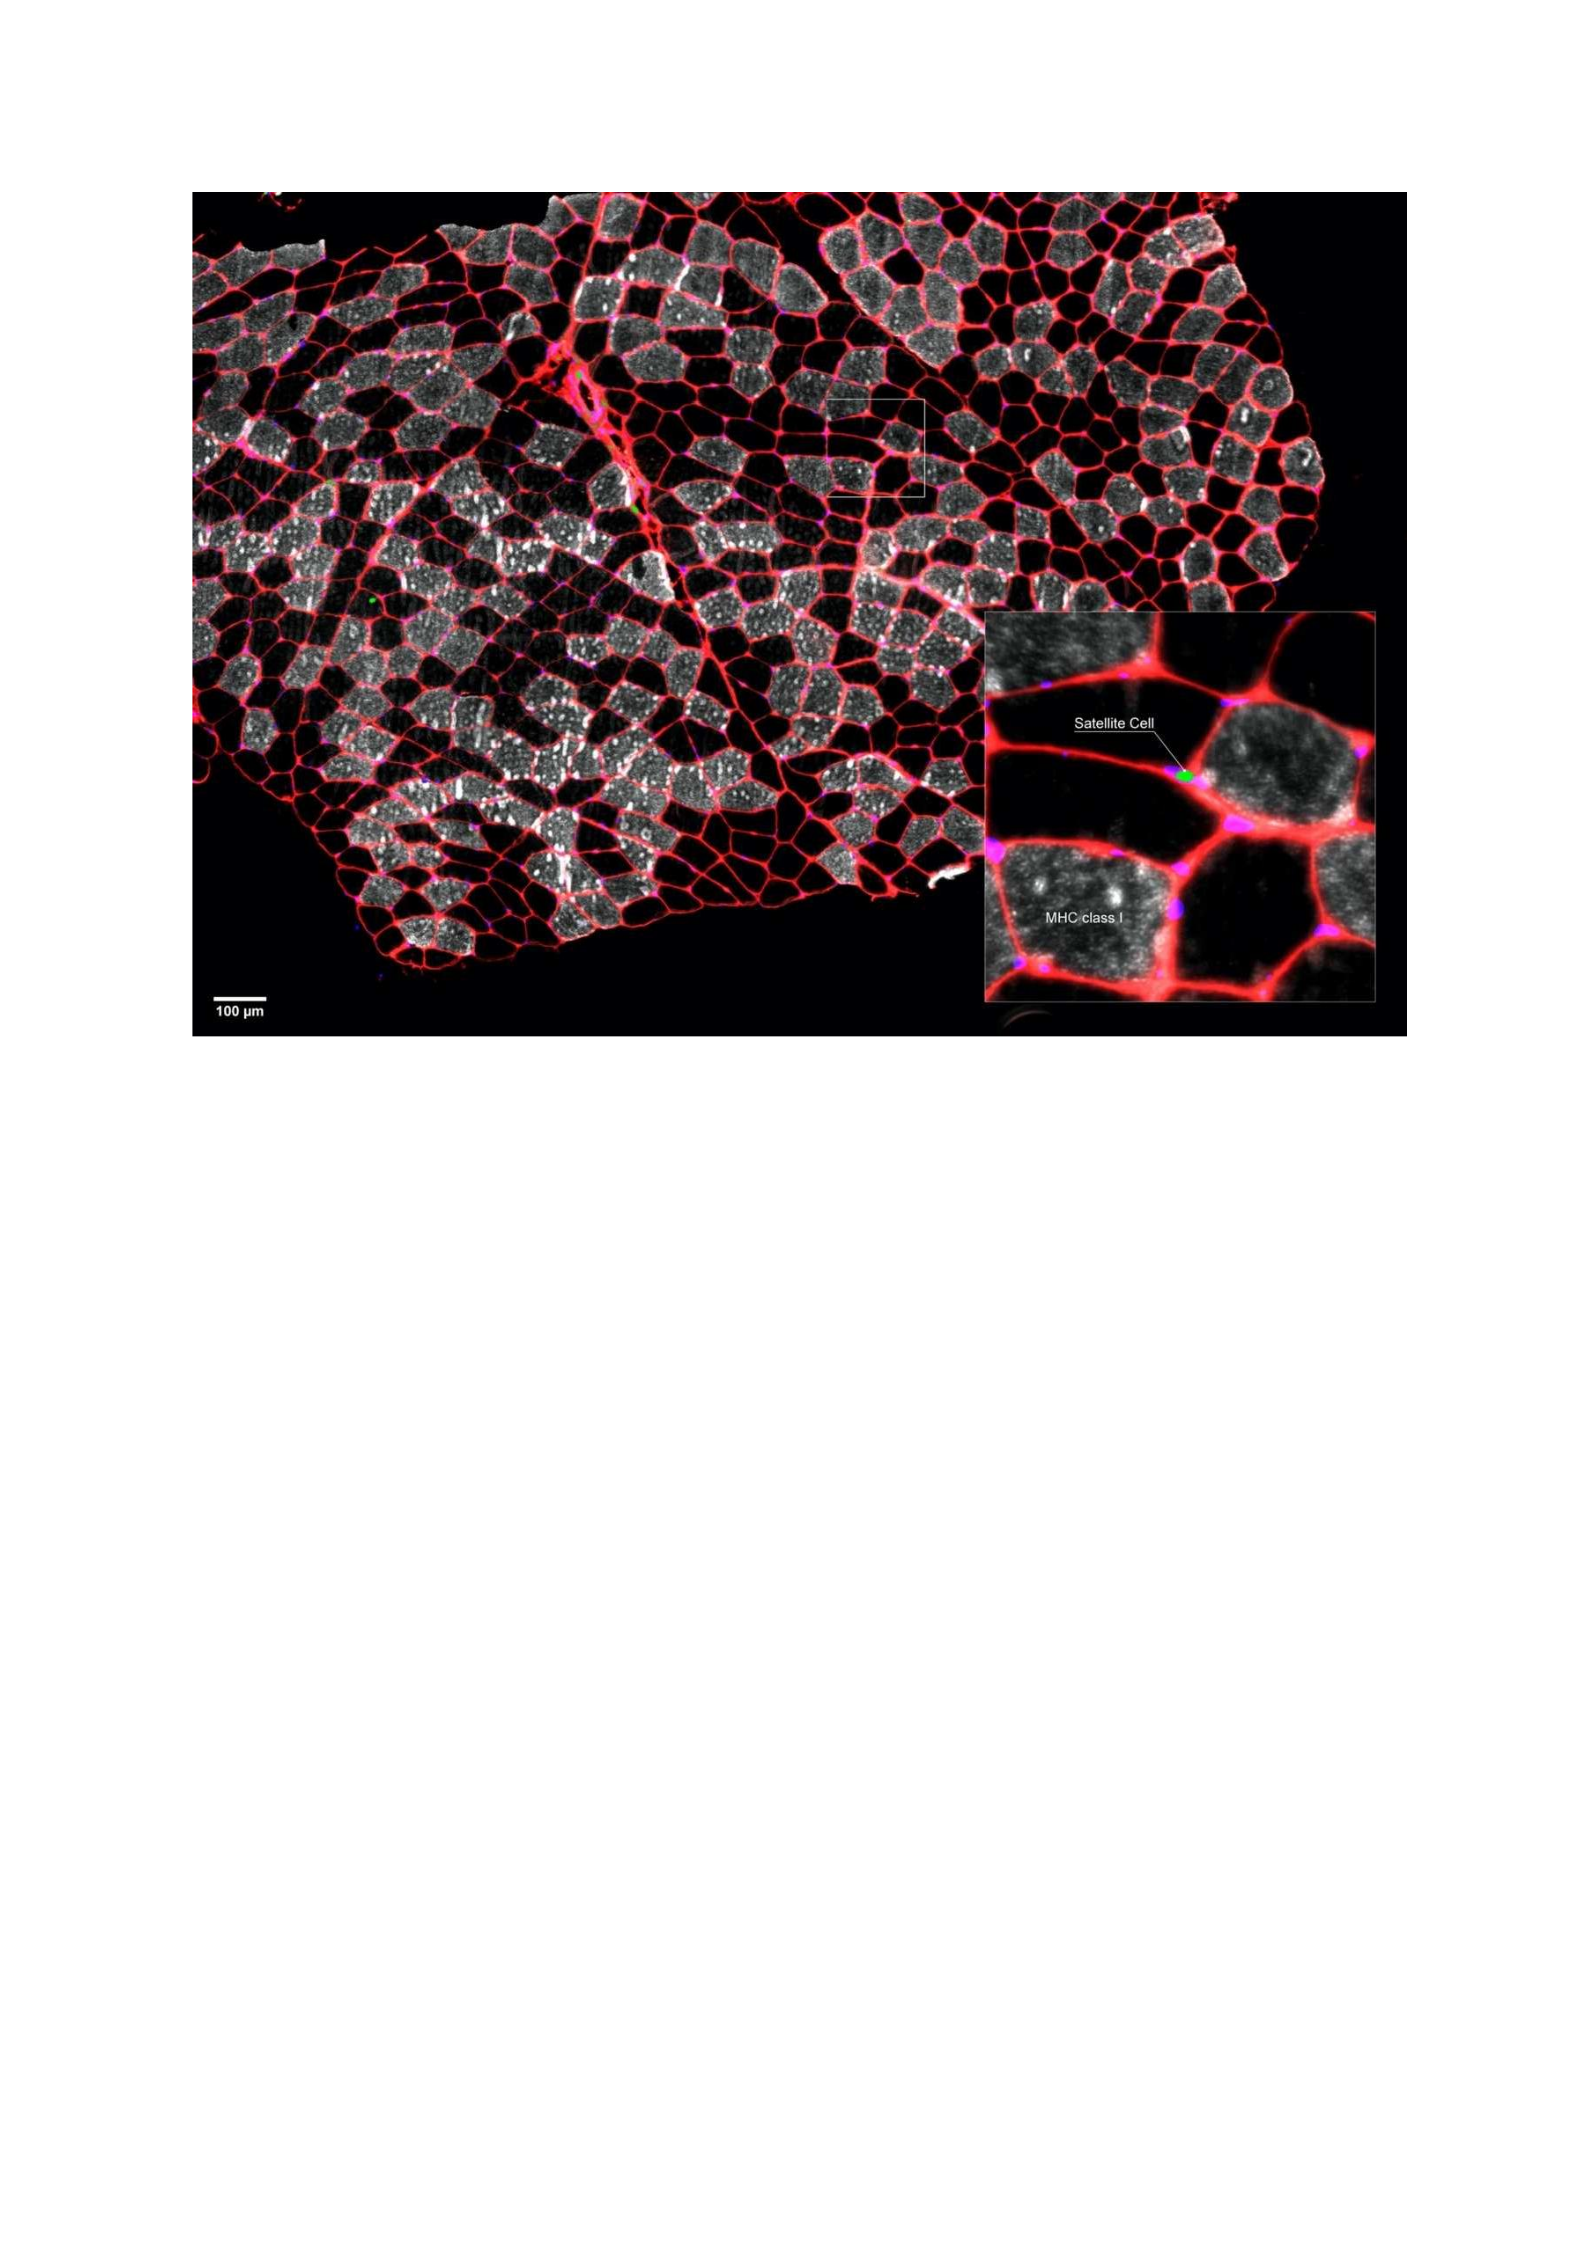
188
Figure 5.6. Representative composite image of a muscle cross-section stained for Pax7 (green),
MHC-I (grey), laminin (red), and nuclei (DAPI; blue). Boxed area is magnified in the bottom
right panel displaying one Pax7+ nucleus (SC).
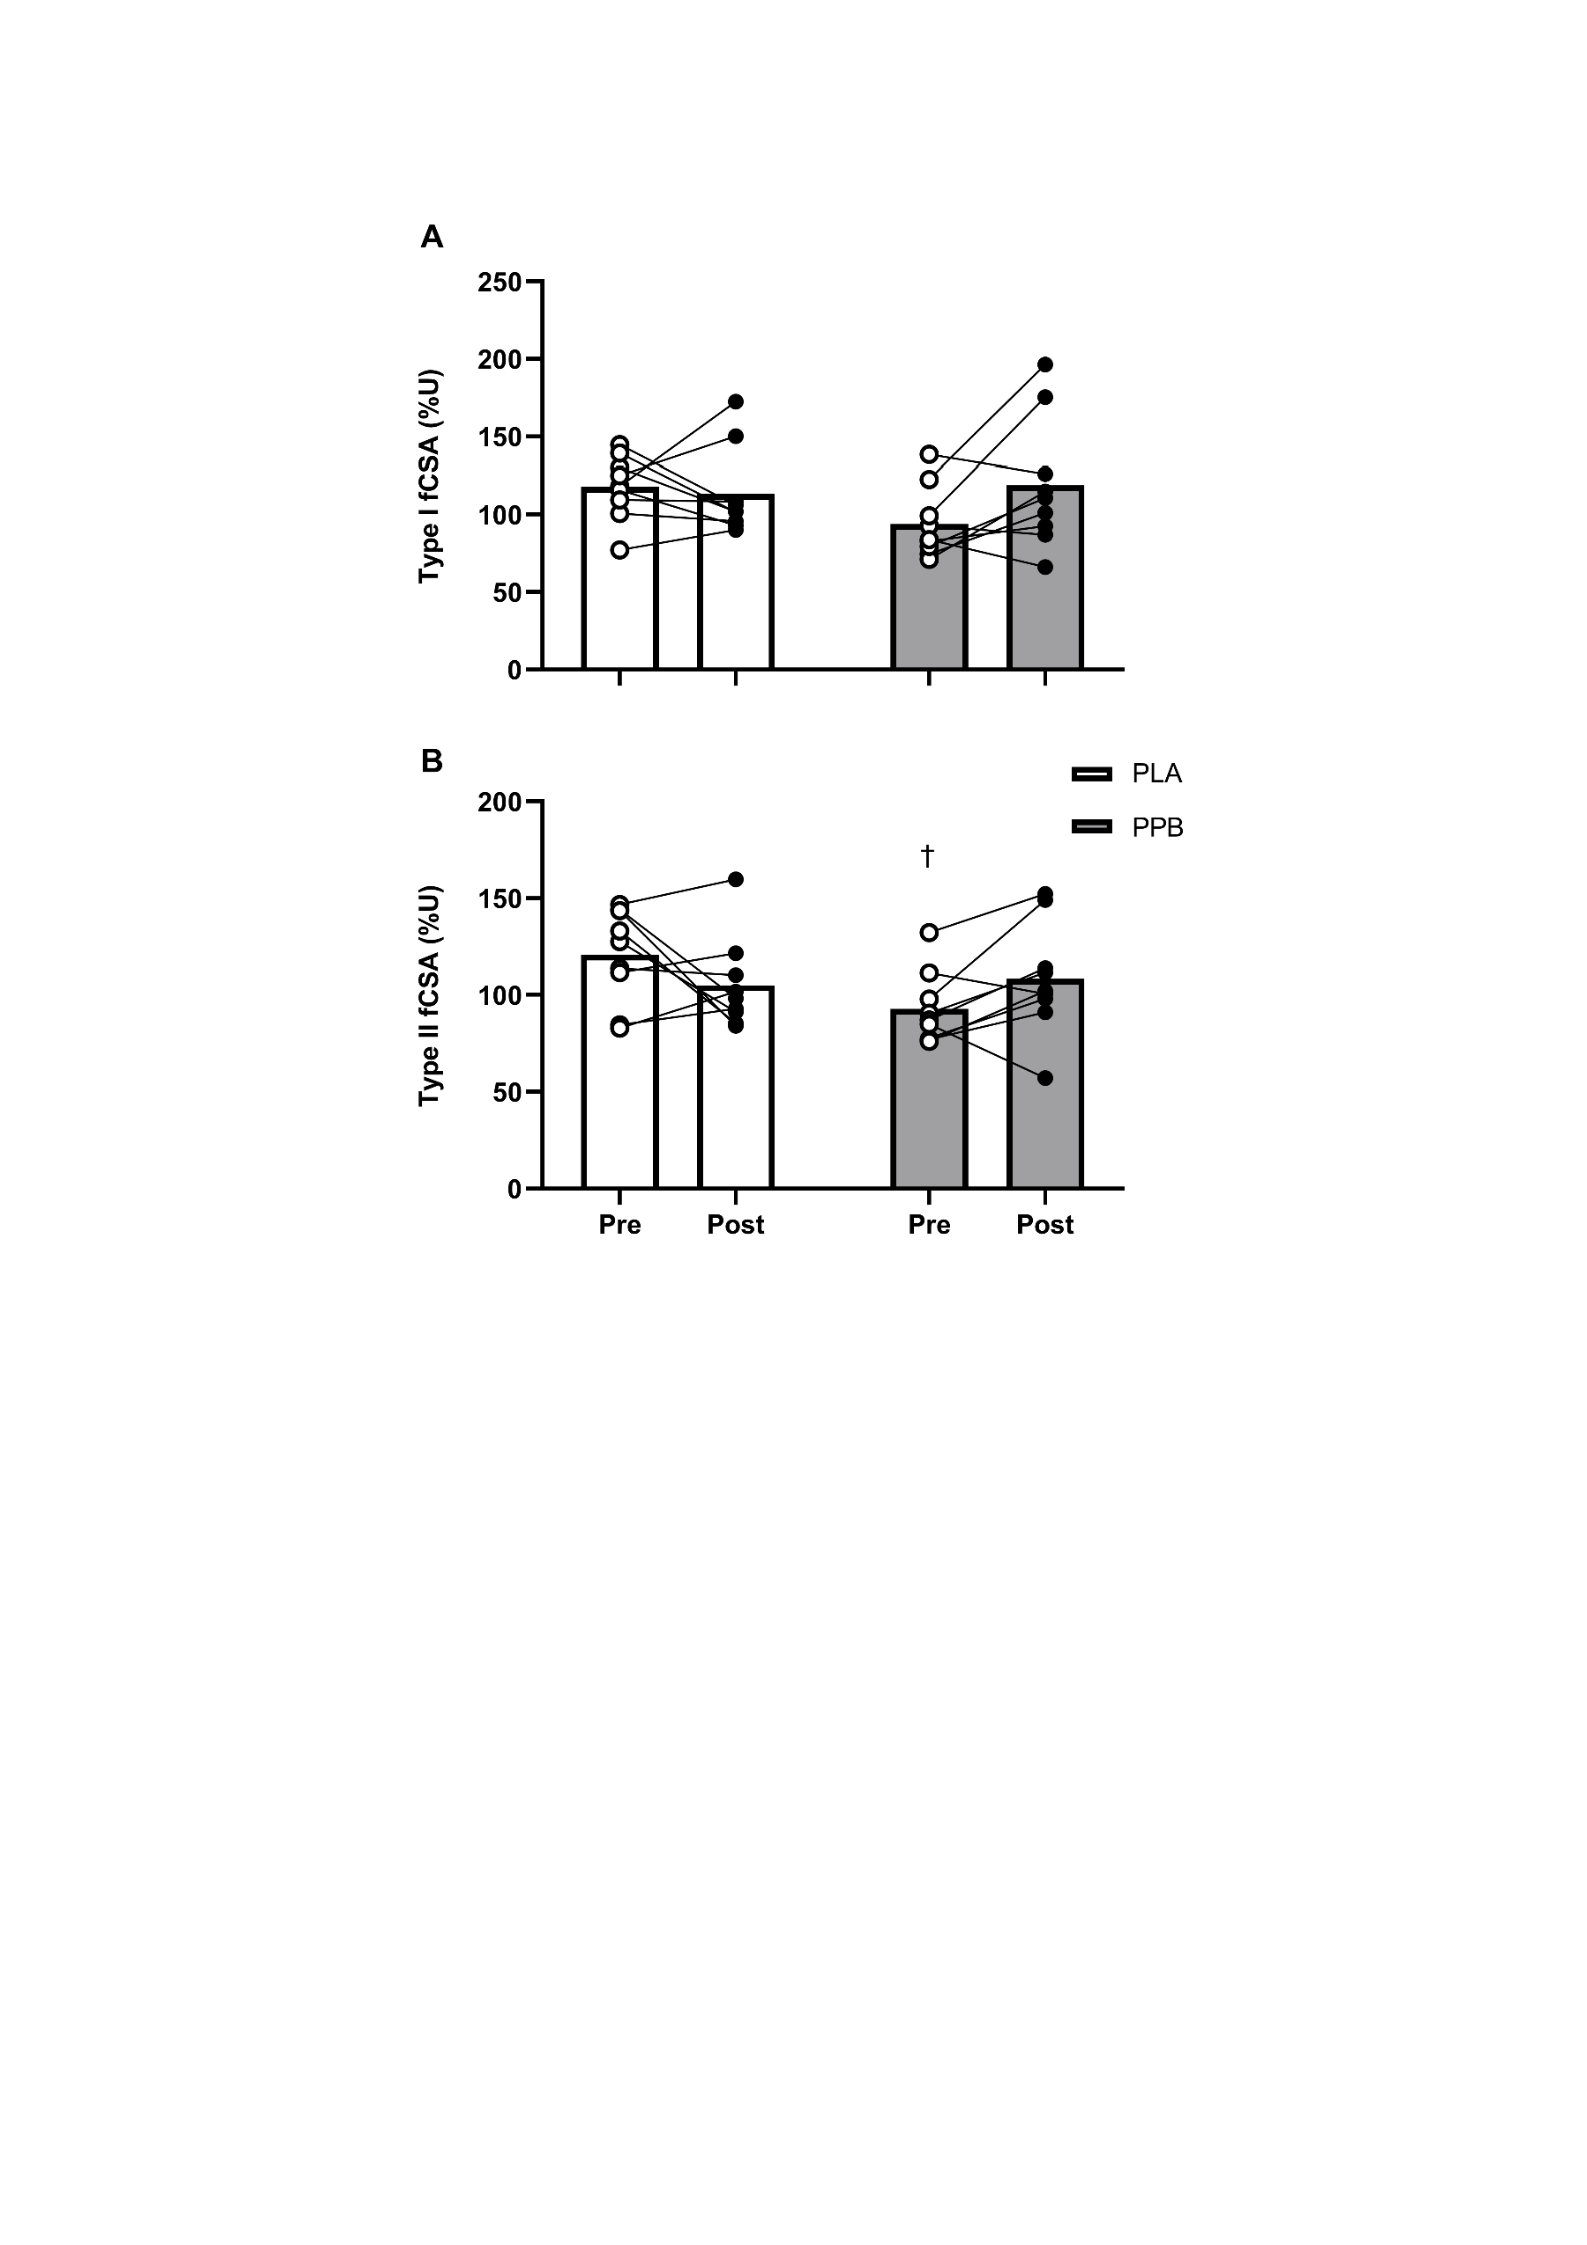
189
Figure 5.7. Muscle fibre cross-sectional area (fCSA) of A: type I; and B: type II; muscle fibres
measured by immunohistochemistry pre (open circles) and post (filled circles) 30 sessions of
unilateral resistance-type exercise training, expressed relative to the untrained leg (%U). A
post-exercise and pre-bed protein-polyphenol (PPB; grey bars) or maltodextrin placebo (PLA;
white bars) nutritional intervention was provided daily. Significant time x group interaction
effect (P < 0.05). Post hoc differences displayed as †P < 0.05 significantly different to PLA
pre-training.
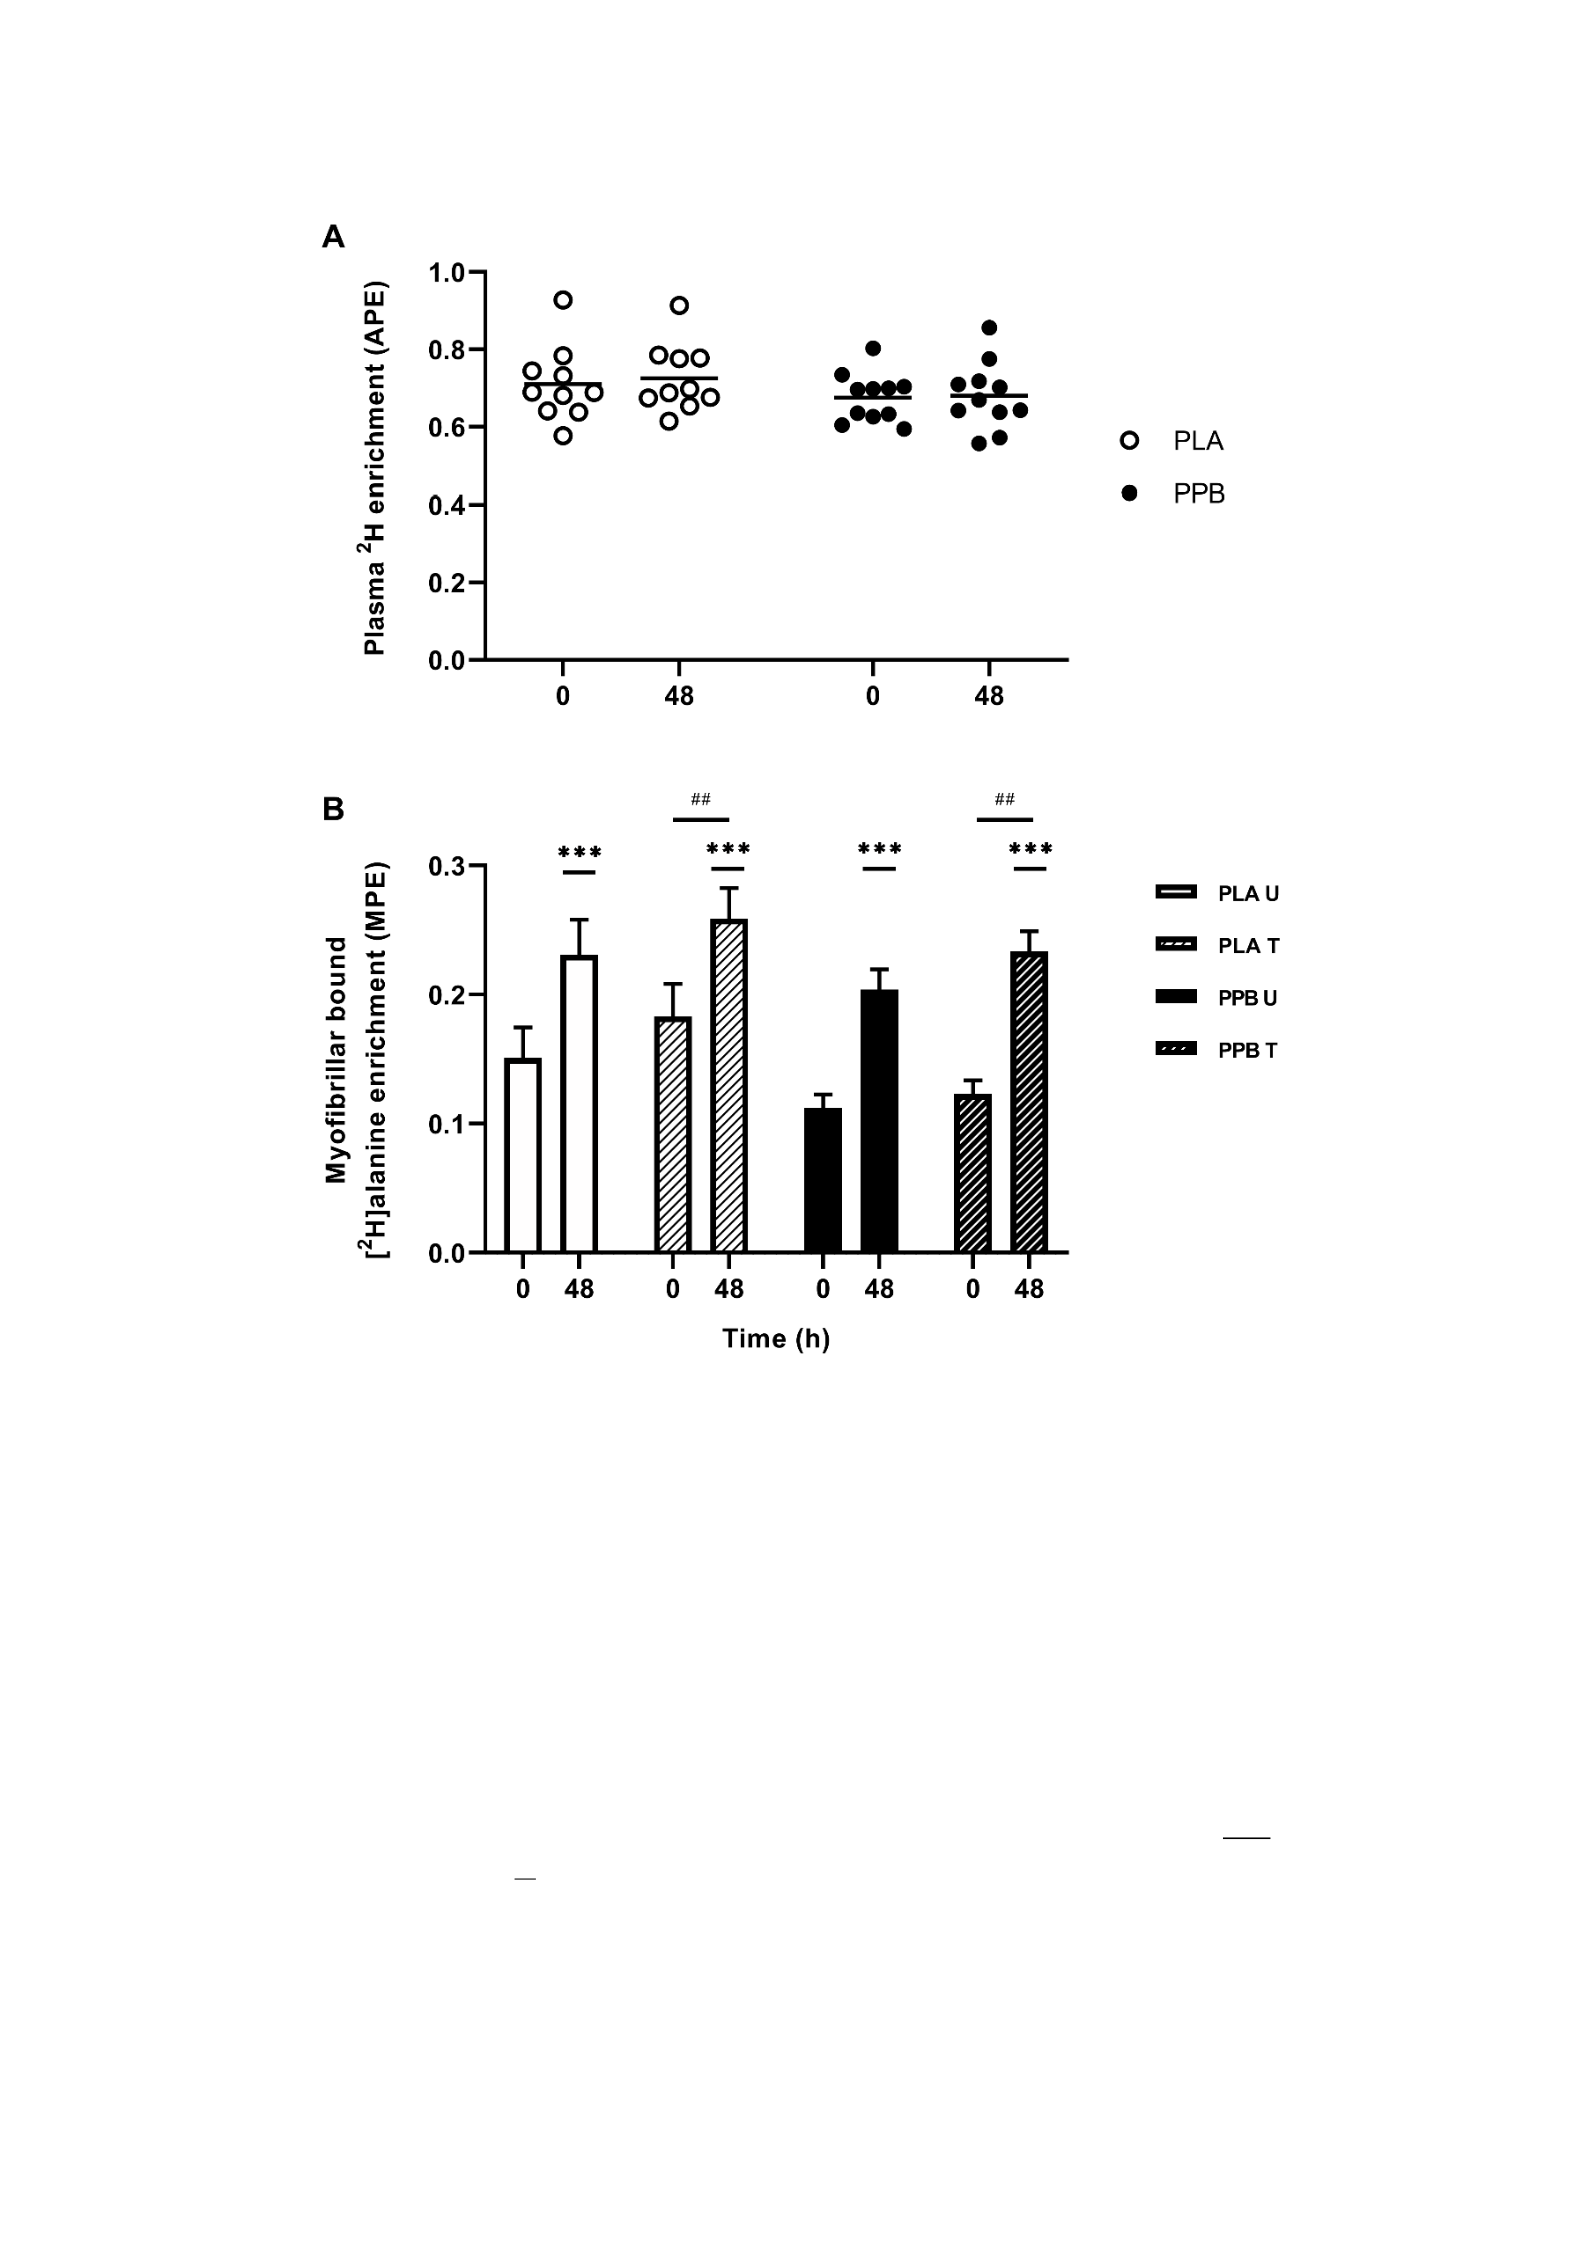
190
Figure 5.8. A: Daily plasma 2H enrichment (%) following oral 2H2O ingestion, measured pre
(0 h) and post (48 h) the first session of unilateral resistance-type exercise. A post-exercise and
pre-bed protein-polyphenol (PPB; n = 10; filled circles) or maltodextrin placebo (PLA; n = 10;
open circles) nutritional intervention was consumed daily. B: Enrichment of myofibrillar bound
[2H]-alanine (MPE) in skeletal muscle biopsy samples obtained at the same time in the trained
(T; hashed bars) and untrained (U; solid bars) legs. A post-exercise and pre-bed protein-
polyphenol (PPB; n = 10; filled bars) or maltodextrin placebo (PLA; n = 10; open bars)
nutritional intervention was consumed daily. B: significant main effect of time (***P < 0.001
different to 0 h) and leg (##P < 0.01 different to U).
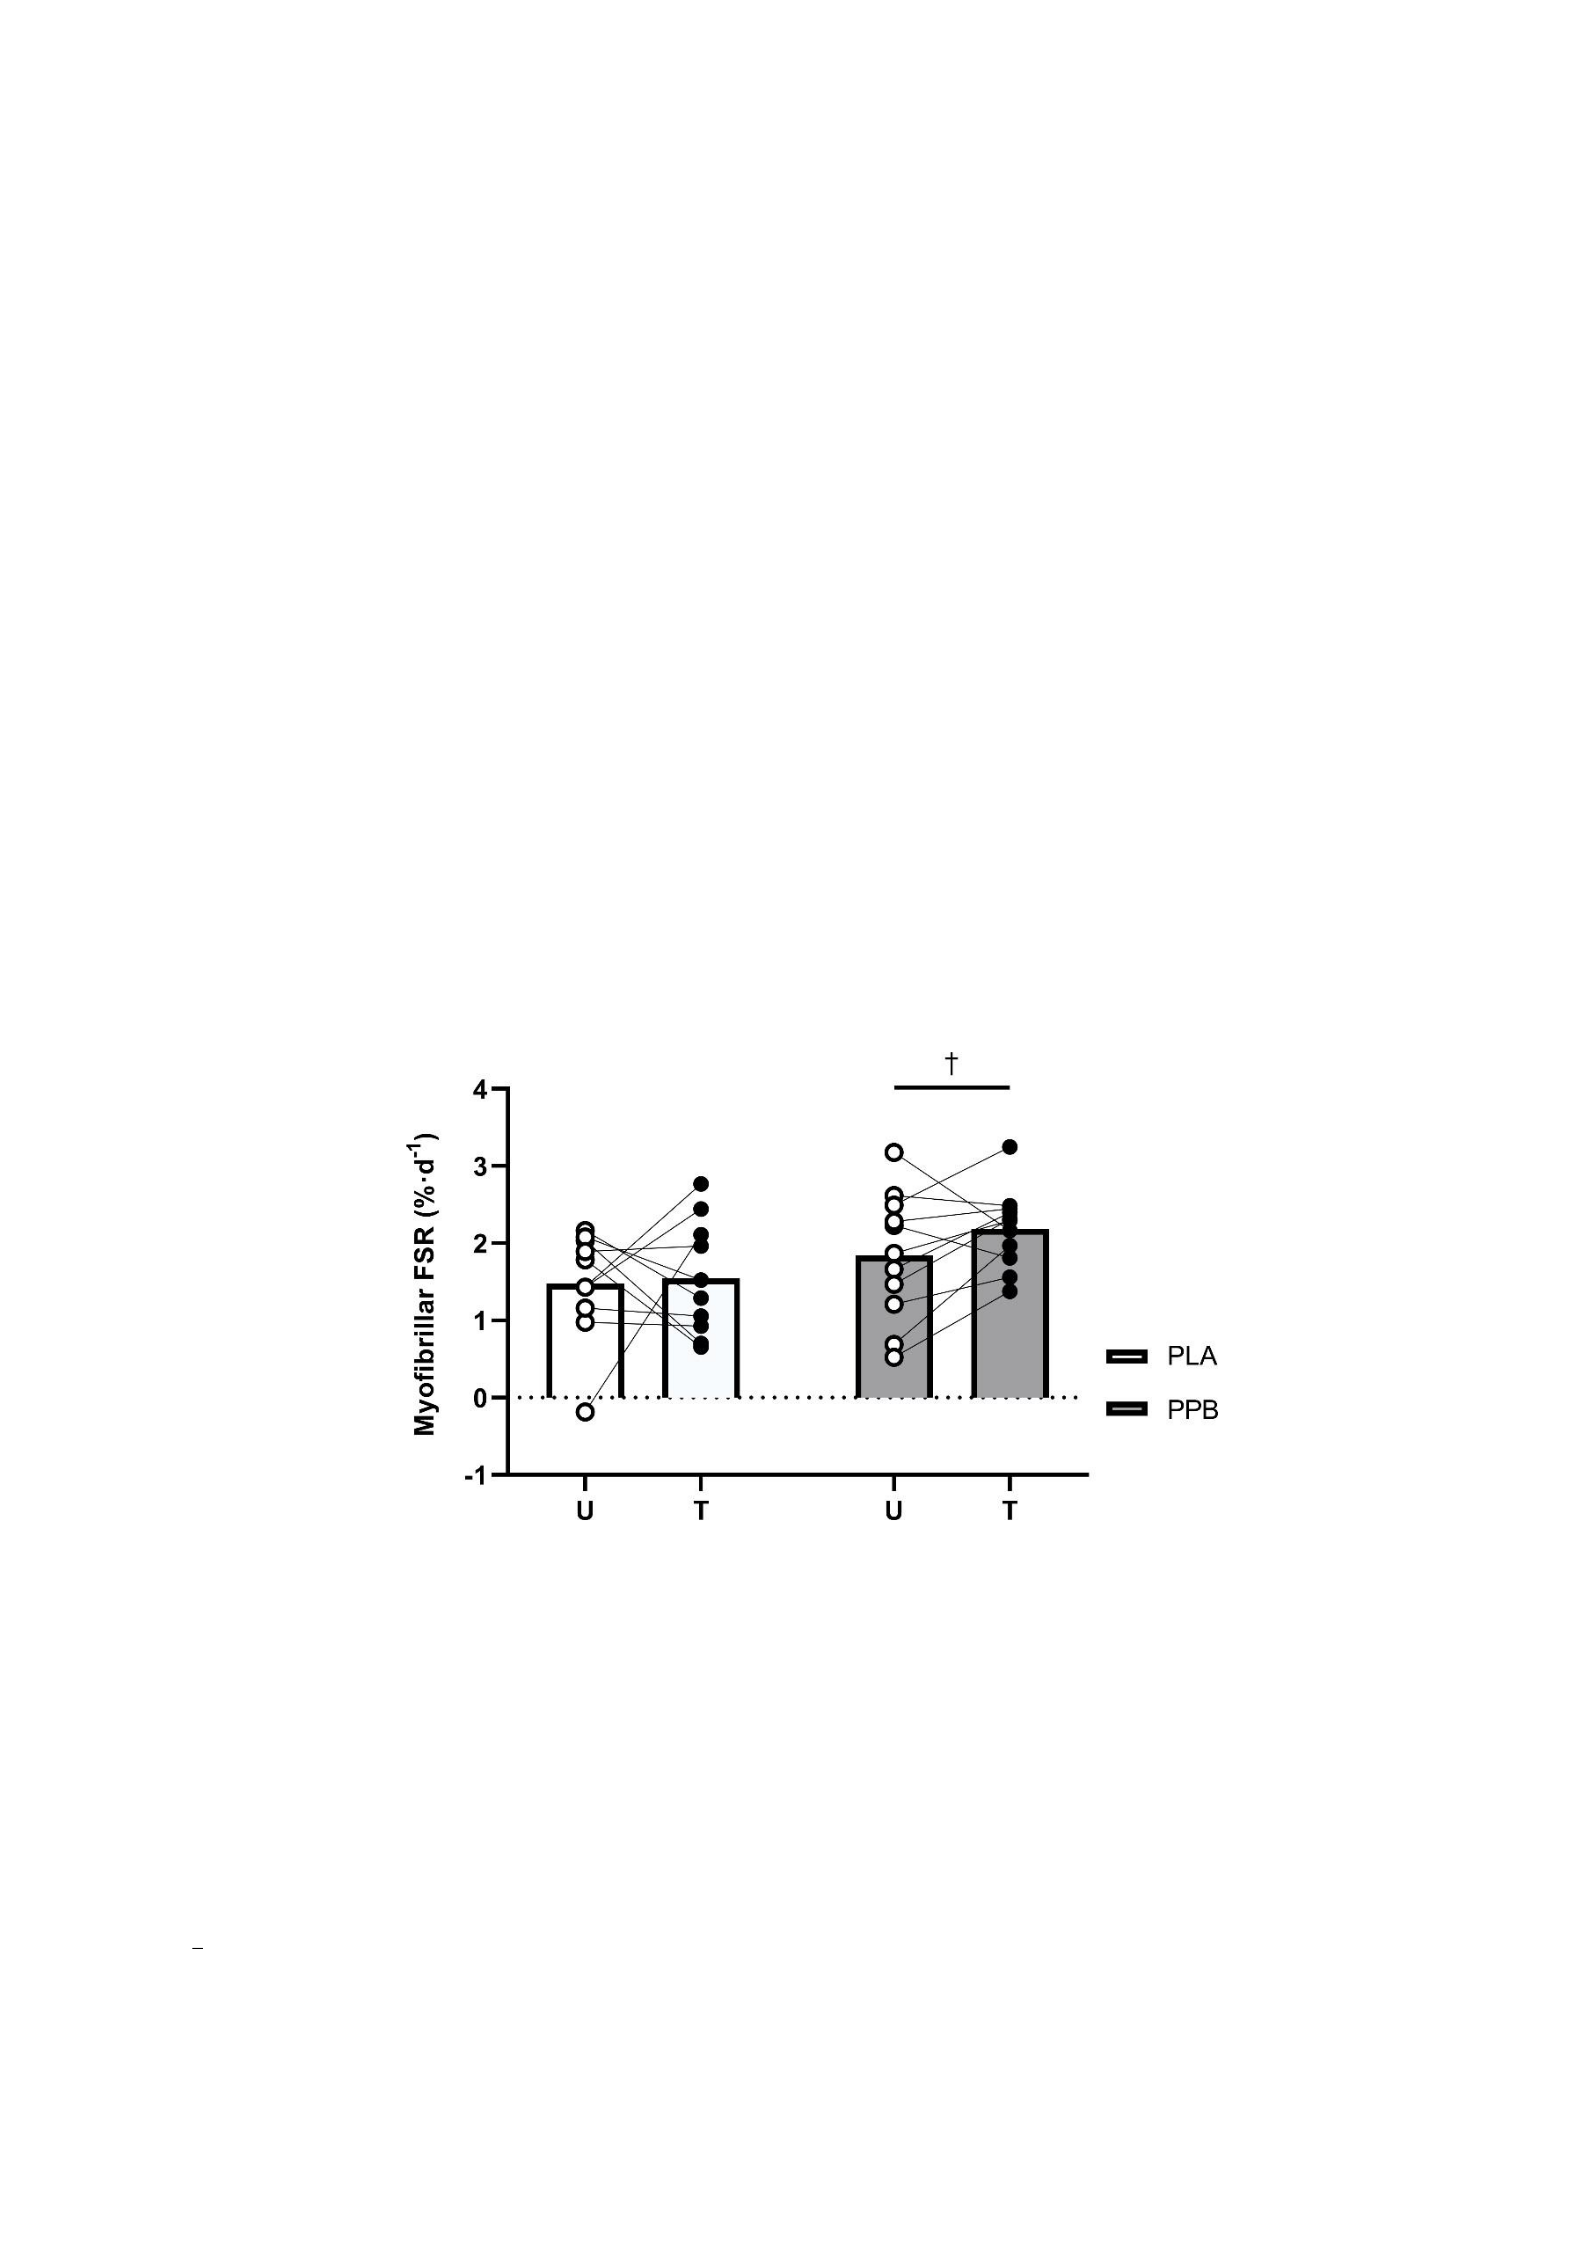
191
5.4.6
Myofibrillar protein synthesis
Following consumption of deuterated water, plasma deuterium enrichment was 0.72 ± 0.02 and
0.68 ± 0.02 atom per cent excess (APE) in PLA and PPB respectively, with no differences over
time or between groups (Figure 5.8A).
Myofibrillar protein-bound [2H]-alanine enrichments increased over time (P < 0.001) but were
unaffected by PPB (Figure 5.8B). At 0 h, the mean myofibrillar protein-bound [2H]-alanine
enrichment was 0.130 ± 0.012 and 0.150 ± 0.014 in U and T legs, rising to 0.216 ± 0.015 and
0.245 ± 0.014 MPE in U and T at 48 h (time effect P < 0.001). Enrichments were significantly
greater in T than U legs (PLA: 22 ± 8%; PPB 14 ± 4%; leg effect P < 0.01), but this was
unaffected by PPB.
Figure 5.9. Free-living, cumulative myofibrillar protein fractional synthesis rate (FSR;
expressed as %·d-1) over 48 h following the first session of unilateral resistance-type exercise
in the trained (T; filled circles) and untrained (U; open circles) legs. A post-exercise and pre-
bed protein-polyphenol (PPB; n = 10; grey bars) or maltodextrin placebo (PLA; n = 10; white
bars) nutritional intervention was consumed daily. Fractional synthetic rates calculated from
plasma deuterium enrichment as precursor pool. Significant main effect of group, denoted by
†P < 0.05 significantly different to PLA.

192
Plasma deuterium enrichment was used as the precursor pool to calculate myoFSR from the
change in myofibrillar protein-bound [2H]-alanine enrichment between 0 and 48 h (Figure 5.9).
In PLA, mean myoFSR was 1.51 ± 0.16 %·d-1 across legs. This was significantly greater with
PPB, increasing to 2.01 ± 0.15 %·d-1 (P < 0.05). However, no differences were observed
between U and T legs.
5.4.7
Correlation analysis
There were no correlations between MyoPS measured following the onset of training and pre-
training strength (r = 0.052, P = 0.83) or function (r = -0.133, P = 0.58). Figure 5.10 displays
correlations between MyoPS and training outcomes. No significant correlations were found
between MyoPS and strength after the first 10 sessions (strength: r = 0.161, P = 0.50), whereas
function tended towards significance (r = 0.420, P = 0.07). However, post-training measures
of function (r = -0.056, P = 0.82) were unrelated to initial MyoPS, whereas a trend for an
inverse relationship was observed for strength (r = -0.434, P = 0.06). Furthermore, no
significant correlations were found between MyoPS and change in total fCSA (n = 17; r =
0.317, P = 0.21) or type I fCSA (r = 0.323, P = 0.21), whereas a trend for type II fCSA was
observed (r = 0.306, P = 0.09).
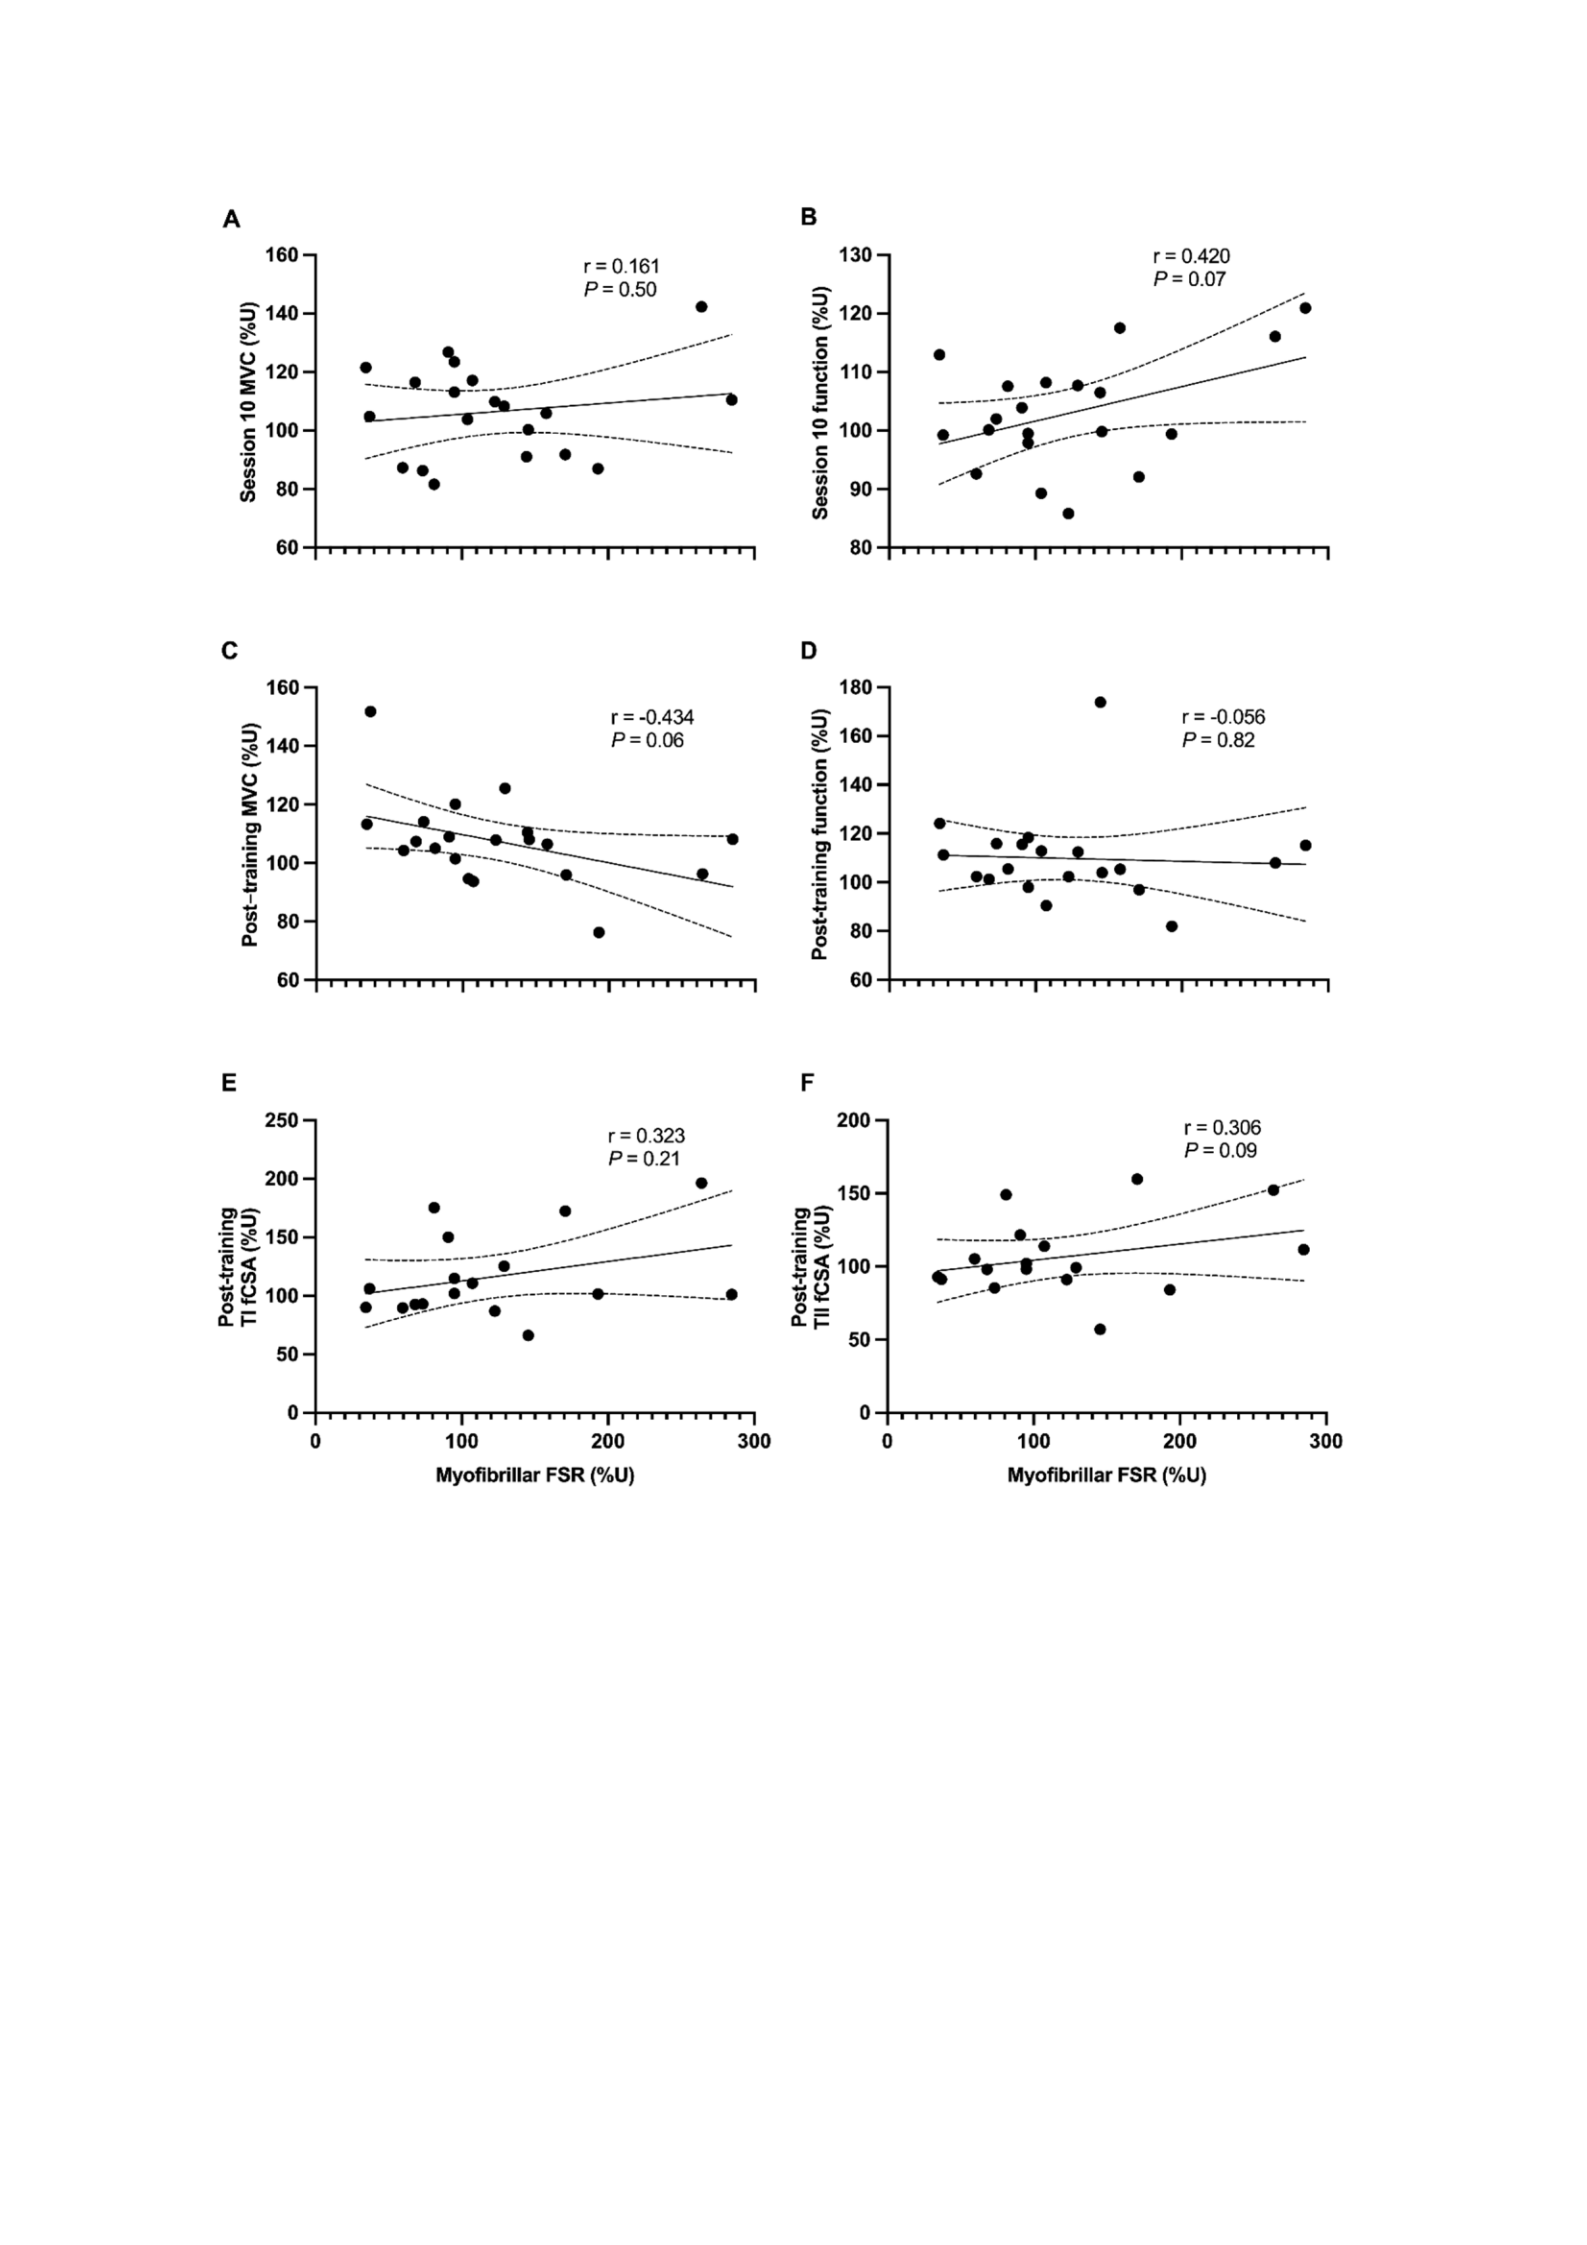
193
Figure 5.10. Correlations between 48 h myofibrillar protein fractional synthesis rate (FSR)
measured in response to the first resistance-type exercise training session and A: strength after
10 sessions, defined as maximal voluntary isometric contraction (MVC); B: muscle function
after 10 sessions; C: strength after 30 sessions (post-training); D: function after 30 sessions
(post-training); E: type I muscle fibre cross-sectional area (fCSA); D: type II fCSA. All data
expressed relative to contralateral, untrained control leg (%U). For A, B, C and D n = 21; E and
F n = 17. Data analysed by Pearson’s correlation analyses. Pearson’s r and P-value displayed
on each graph.

194
5.5
Discussion
In the present study it was hypothesised that a daily post-exercise and pre-bed PPB nutritional
intervention would accelerate recovery from damage following the onset of RET, thereby
increasing rates of MyoPS and accelerating improvements in muscle strength, function and
muscle fibre size both over 10 and 30 sessions of RET in healthy males and females. Post-
exercise and pre-bed consumption of PPB increased daily rates of MyoPS by ~33% over 48 h
after the first training session versus placebo. Corrected to the untrained leg, PPB increased
muscle function ~7% over the first 10 training sessions, whereby a trend (P = 0.07) for a
moderate correlation was observed between daily rates of MyoPS and muscle function at
session 10. However, PPB did not potentiate the improvement in muscle strength at session 10,
nor the improvement in strength and function measured post-training. Rates of improvement
in total, concentric and eccentric training volumes were greatest over the early phase of training
(sessions 1-10) but were unaffected by PPB. PPB increased mean fCSA with training, with this
change driven primarily by type II fibres. Together, these data are the first to show that
increasing rates of MyoPS with PPB accelerates early improvements in muscle function during
RET and supports type II fibre hypertrophy.
A prolonged period of RET increases muscle strength and exercise capacity (Damas et al.,
2019; Lemon et al., 1992; MacDougall et al., 1980; Mayhew et al., 2009; Snijders et al., 2015).
Thirty sessions of unilateral RET employed in the present study increased isometric muscle
strength by ~8% (Figure 5.2A) and isokinetic muscle function by ~11% (Figure 5.2B).
Furthermore, total work performed during training increased by ~27% from the first to the last
session (Figure 5.4A). Interestingly, eccentric training volume increased significantly earlier
than concentric (session 4 vs. session 20), which may be a result of early remodelling directed
at promoting fascicle length, thereby enabling greater ability to withstand mechanical stretch
(Franchi et al., 2015; Timmins et al., 2016). During the first 10 sessions, comprising the early

195
phase of training (~3 weeks after onset of RET), rate of increase in total, concentric and
eccentric training volume was greatest, compared to the middle (sessions 11-20) and/or late
(sessions 21-30) phases. Moreover, MVC strength increased ~8% as analysed over the first 10
sessions, indicating that the majority of contractile improvement occurred over the first 3 weeks
of training. In agreement with these findings, ~60% of the gains in total training volume or 1-
repetition max (1-RM) occur within the first 3-4 weeks of a 6 (Brook et al., 2015), 8 (Damas
et al., 2019) or 12 (Snijders et al., 2015) week resistance training program.
Nutritional strategies known to increase muscle protein synthesis following resistance exercise
(Tang et al., 2007; Wilkinson et al., 2007) potentiate improvements in muscle size and strength
during RET versus carbohydrate or noncaloric placebo (Hartman et al., 2007; Snijders et al.,
2015). Here, we show for the first time that a post-exercise and pre-bed protein polyphenol
beverage significantly increases rates of MyoPS over 48 h following training, coinciding with
~7% greater muscle function during ~3 weeks of RET (Figure 5.3B), with a trend for a positive
relationship (r = 0.42, P = 0.07) between rates of MyoPS and function as measured at session
10 (Figure 5.10B). Greater quantities of myofibrillar protein synthesised in response to a single
bout of RET might partly explain why the greatest rate in functional improvement occurs
within ~3 weeks of training (Brook et al., 2015; Damas et al., 2019; Hakkinen et al., 1998;
Snijders et al., 2015). That is, in the untrained state, rates of MyoPS are upregulated for at least
24 h following resistance exercise (Tang et al., 2008), culminating in greater rates of MyoPS
measured over 48 h versus when trained (Damas et al., 2016b). The use of PPB served to
promote MyoPS further, possibly increasing the absolute quantity of myofibrillar protein in the
muscle, which may explain the acceleration of functional improvements over 10 sessions.
Should rates of MyoPS explain training outcomes, and should rates fall with training, the
culmination of MyoPS after RET in both ‘untrained’ and ‘trained’ states may ultimately
determine the eventual magnitude of improvements. Given that function did not differ between

196
groups at the end of training in the present study, PPB may have accelerated the transition to a
‘trained’ phenotype such that the decrease in MyoPS in response to an isolated bout of exercise
occurred sooner than in PLA. For this suggestion to be true, however, daily rates of MyoPS
with PPB in the ‘trained’ state would presumably have to be lower than rates of MyoPS in the
‘untrained’ state in PLA. These suggestions require further experimental verification, as no
studies to our knowledge measure rates of MyoPS during training with protein and/or
polyphenol consumption.
In contrast to muscle function, RET increased strength in both groups over 10 sessions and the
effect of protein was not observed. This is supported by work presented elsewhere, where
supplementation with 20 g protein per day did not improve gains in muscle strength, assessed
by 1-RM or power output during a maximal countermovement jump pre and post 4 weeks of
RET (Boone et al., 2015). Indeed, increases in strength may be reflective of the rapid
neurological adaptations that are prominent in the first 2-3 weeks of training (Hakkinen et al.,
1998; Seynnes et al., 2007), potentially masking any influence of protein and MyoPS.
Supporting this discordance, Chapter 4 demonstrated that PPB accelerated the improvement in
muscle function but not peak isokinetic torque following damaging eccentric exercise.
Moreover, others have demonstrated that protein ingestion has no influence on 1-RM or peak
torque over 4 weeks of RET suggesting that 1-RM and/or maximum torque assessments are
less sensitive to protein ingestion over the short term (Boone et al., 2015; Lemon et al., 1992).
Of interest, a trend for an inverse relationship was observed between MyoPS and strength after
30 sessions (r = -0.434, P = 0.06; Figure 5.10C). The direction of this relationship is surprising,
given that meta-analyses support greater protein intakes to further increase strength during
typical resistance training protocols (Cermak et al., 2012; Morton et al., 2018). However,
strength, as measured in the present study, was determined as isometric peak torque during an
MVC, whereas the effects of protein are observed with 1-RM (Cermak et al., 2012; Morton et

197
al., 2018). Specifically, a meta-analysis of studies assessing strength by isometric or isokinetic
peak torque reveals no effect of protein (Morton et al., 2018), in support of the present findings.
Whilst this has been attributed to lack of congruity between strength assessment and training
modality (Buckner et al., 2017), such that familiarity with the testing protocol is required to
detect strength gains (Dankel et al., 2020), MVC testing in the present study was repeated every
3 sessions (approximately weekly) throughout training and so participants were presumably
not naïve to the measure. Thus, whether MVCs accurately represent muscle protein accretion
requires further attention, as will be discussed in more detail in Chapter 6.
In the present study, type II fCSA increased ~17% over the training period with PPB only, as
has been observed elsewhere (Andersen et al., 2005; Bird, Tarpenning, & Marino, 2006; Farup
et al., 2014b; Hartman et al., 2007; Snijders et al., 2015). Whilst whole muscle CSA correlates
with muscle strength in both young and old populations (Maughan, Watson, & Weir, 1983;
Verdijk et al., 2010), RET at low intensities can induce hypertrophy without concomitant
strength gains (Schoenfeld, Grgic, Ogborn, & Krieger, 2017). Furthermore, increases in
strength can occur independently of increases in fCSA in response to both 12 and 24 weeks of
RET (Churchward-Venne et al., 2015). Interestingly, ~18-26% greater fCSA has been reported
with consumption of milk, soy, whey, or a mixed protein blend over RET, without promoting
strength gains over the effects of RET alone (Andersen et al., 2005; Farup et al., 2014b;
Hartman et al., 2007), supporting the present findings. Thus, it appears that these processes are
not inextricably linked, likely due to differences in the underlying physiology. As discussed
above, strength gains may be explained partly by neural adaptations (Aagaard, Simonsen,
Andersen, Magnusson, & Dyhre-Poulsen, 2002; Bernardi, Solomonow, Nguyen, Smith, &
Baratta, 1996), whereas muscle growth will be influenced by muscle protein accretion
(Goldberg, 1968; Laurent et al., 1978). Interestingly, there was a trend (r = 0.3, P = 0.09) for a
moderate relationship with MyoPS and type II hypertrophy measured after 30 training sessions,

198
suggesting that type II fibre hypertrophy is partly mediated by MyoPS. At the same time, these
data would suggest that myofibrillar synthesis is not the sole process underpinning
hypertrophy. Recent evidence suggests that high volume resistance exercise may induce
sarcoplasmic hypertrophy, particularly the expression of protein signalling pathways related to
glucose metabolism in the muscle (Haun et al., 2019). Whether protein ingestion supports the
expansion of the sarcoplasmic pool during training therefore requires further attention.
That early rates of MyoPS contribute to RET adaptations is in contrast to recent work (Damas
et al., 2016b; Mitchell et al., 2014). Transient muscle damage is observed following the onset
of RET (Damas et al., 2016b; Damas et al., 2016c) and can manifest as greater muscle soreness
and reduced contractile ability (Vissing et al., 2008). Indeed, the discordance between rates of
MyoPS captured following the onset of training and resultant RET adaptations is hypothesised
to be due to the existence of muscle damage, with MyoPS thought to reflect greater demand
for muscle repair (Damas et al., 2016b; Mitchell et al., 2014). However, Chapter 4
demonstrated that in the presence of muscle damage, PPB is unable to further stimulate MyoPS
between 24 – 72 h of recovery, in contrast to the present findings between 0 – 48 h. While we
observed an increase in muscle soreness in response to the first training session in both groups,
training did not impair muscle strength or function (Figure 5.3B), which would be expected in
the presence of muscle damage (as evidenced in Chapter 4). Moreover, we have demonstrated
that the nutritional strategy applied herein accelerates recovery from muscle-damaging
eccentric exercise (Jameson et al., 2021). Additionally, there were no group differences in
cumulative work performed in training over the first 4 and 10 training sessions, corresponding
to the duration of functional impairment in Chapter 4 and the duration of muscle damage
following the onset of training, as indicated by Z-line streaming (Damas et al., 2016b),
respectively. Therefore, it is unlikely that muscle damage was induced by training in the present
study. Yet, when fCSA was analysed irrespective of fibre type, the present data mirror the

199
findings of Damas et al. (2016c), by demonstrating no relationship between initial MyoPS and
post-training mean fCSA. Given the additional resolution provided by the present study
regarding fibre type-specific adaptations, these data are the first to counter the suggestion that
MyoPS following the onset of training is reflective of muscle damage, but instead, demonstrate
that MyoPS is partly attributable for fibre type and exercise specific adaptations.
Muscle fibre CSA reportedly correlates with satellite cell content (Verdijk et al., 2010) and a
period of RET increases the number of satellite cells associated with both type I and type II
muscle fibres (Bellamy et al., 2014; Karlsen et al., 2020; Mackey, Andersen, Frandsen, &
Sjogaard, 2011a; Mackey et al., 2011b; Snijders et al., 2016). In particular, the increase in
satellite cell content per myofibre appears related to the increase in fCSA (Bellamy et al., 2014;
Snijders et al., 2016). Furthermore, the rapid increase in satellite cell content 72 h after the
onset of RET correlates with the resultant increase in muscle CSA when measured after 16
weeks (Bellamy et al., 2014), suggesting that satellite cell expansion underpins RET-induced
increases in fCSA. However, contrary to these data, there was no increase in satellite cell
content per myofibre over time, or between trained and untrained legs at any time point.
Furthermore, we observed no effect of PPB on any of these parameters, suggesting that
expansion of the satellite cell pool is not a requirement of muscle fibre hypertrophy. In support
of these findings, Mackey et al. (2011b) observed a ~24% increase in satellite cell numbers
expressed relative to fibre number after a 12-week RET program, but both type I and type II
fCSA were unchanged. This was replicated by a subsequent study (Karlsen et al., 2020), where
it was also observed that an acute bout of 200 electrically-stimulated eccentric contractions
performed in one leg pre-training caused a ~2-fold increase in satellite cell content, without
further augmenting any RET adaptations. Indeed, the reported increase in satellite cell content
may have been reflective of earlier muscle damage (Karlsen et al., 2020), as long-term
increases in satellite cell content have been observed after 30 days after a single bout of

200
eccentric exercise in humans (Mackey et al., 2016), and up to 3 months following toxin
injection in mice (Hardy et al., 2016). In line with this mechanism, it is unsurprising that we
did not observe an increase in satellite cell content given that we did not observe any evidence
of muscle damage following the onset of RET.
In conclusion, these data show that PPB increases daily rates of MyoPS following the onset of
training, and that by using a unilateral training model allowing for intra-individual time-
matched control to reduce heterogeneity in outcomes, these data provide a novel insight into
the time course of resistance training adaptations by revealing that PPB accelerated the
improvement in muscle function relative to isocaloric placebo after 10 sessions of training.
Given that a trend for a positive relationship was observed between these variables, these data
suggest that MyoPS may determine early functional improvements. As the placebo group had
improved to a similar extent post-training, PPB may have accelerated the transition to a
“trained” phenotype with regards to MyoPS, which requires further attention. Extending on
previously published data by providing greater resolution into the fibre type adaptive process,
the observation that PPB also increased type II fibre hypertrophy after 30 sessions supports a
role of MyoPS in this process. Nonetheless, correlations were not strong and MVC strength
and type I hypertrophy were not potentiated with PPB, highlighting that multiple factors likely
underpin each outcome.

201
Chapter 6 - General Discussion

202
The overarching hypothesis of this thesis was that protein and polyphenol supplementation
would provide a sufficient anabolic milieu to accelerate recovery from muscle damage through
increasing MyoPS and dampening inflammation. It was hypothesised that these processes
would be identified as essential for recovery, and that promoting MyoPS would thereby
accelerate functional recovery and adaptations over a period of resistance-type exercise
training.
Chapter 3 demonstrated that the protein-polyphenol nutritional strategy employed in this thesis
elevated postprandial circulating amino acid concentrations, promoting ~5% greater whole-
body protein synthesis and positive net balance compared to isocaloric placebo. In Chapter 4,
this strategy was then applied to a model of muscle damage where it was hypothesised that this
postprandial anabolic milieu would promote recovery from eccentric exercise. Remarkably,
the nutritional intervention had improved recovery at 48 h when the loss of muscle function
and soreness was the greatest in the placebo group (~36% decline in muscle function). Given
that the contractile myofibrillar proteins are damaged following eccentric exercise (Friden et
al., 1983), and that eccentric exercise stimulates greater rates of myofibrillar protein synthesis
versus concentric (Moore et al., 2005), the greater availability of exogenous amino acids was
theorised to support and enhance the myofibrillar protein synthetic response, and therefore
explain recovery rate. However, contrary to this hypothesis, rates of MyoPS were unaffected
by consumption of protein and polyphenol over a postprandial, overnight, and early stage of
recovery, corresponding to 24 – 27h, 27 – 36 h and 24 – 72 h after muscle damage. Whilst
Chapter 3 also observed similar rates of postprandial MyoPS between intervention and placebo
groups, MyoPS was greater with PPB beyond 72 h following eccentric exercise. Therefore,
these data indicate that recovery is not underpinned by MyoPS, and that MyoPS appears not to
be limited by exogenous amino acid availability. To explore other mechanisms regulating
recovery, including the influence of the polyphenol component of the nutritional intervention,

203
expression of 224 genes selected for their roles in amino acid transportation, apoptosis,
substrate metabolism, inflammation, insulin signalling, protein synthesis and breakdown, as
well as several transcription factors, were analysed. Eccentric exercise increased expression of
pathways related to inflammatory (i.e., ‘TNFR2 non- canonical NF-kB pathway’ and
‘MAP3K8 (TPL2)-dependent MAPK1/3 activation’) and regenerative (i.e., ‘Regulation of
PLK1 Activity at G2/M Transition’) signalling, but these did not differ between group and thus
cannot explain accelerated recovery.
The importance of muscle protein synthesis to hypertrophy has been understood for some time,
whereby greater rates of radio-labelled amino acid incorporation have been observed in
hypertrophying muscles of rodents and fowl (Goldberg, 1968; Laurent et al., 1978). However,
the exact relationship between MyoPS and hypertrophy is unclear; the greatest gains in strength
and muscle cross-sectional area are observed over the first ~3 weeks of training (Hakkinen et
al., 1998; Snijders et al., 2015) when rates of MyoPS are greatest (Brook et al., 2015).
Conversely, others have suggested that rates of MyoPS following the onset of training are
reflective of muscle damage rather than directed towards hypertrophy (Damas et al., 2018;
Damas et al., 2016b), thereby explaining why rates of MyoPS captured at this time do not
correlate with resultant gains in muscle cross-sectional area and volume (Damas et al., 2016b;
Mitchell et al., 2014). As Chapter 4 demonstrated that the protein-polyphenol nutritional
intervention drastically improved recovery from muscle damage and increased MyoPS
thereafter, Chapter 5 investigated whether this approach would support recovery from any
muscle damage, increase MyoPS and further promote adaptations to a training model
employing 30 sessions of unilateral RET, particularly over the first 3 weeks of training. Indeed,
the nutritional intervention increased rates of MyoPS by ~33% versus PLA over 48 h.
Supporting the hypothesis that this would promote adaptations, muscle function improved ~7%
with PPB only at training session 10 (after 3.0 +- 0.1 weeks of training), where a trend for a

204
positive relationship between function and MyoPS was observed (r = 0.420, P = 0.07).
Interestingly, PPB did not influence strength at this time point, nor strength and function
measured post-training beyond the effects of RET alone, suggesting the gains in function were
accelerated rather than further enhanced. Moreover, given the specificity of the adaptations that
were supported by PPB, these data support the contention that RET outcomes are
multifactorial.
The primary findings and specific limitations from these studies are discussed within each
experimental chapter. Therefore, the remainder of this chapter will address common themes to
all studies and highlight areas for further research.
6.1
A novel dosing strategy for deuterium oxide
A novel deuterium oxide dosing strategy was presented in Chapter 2 and applied to the studies
in Chapter 4 and 5, based on the assumption that the body water pool contributes 70% body
mass in healthy lean individuals (Watson et al., 1980) and turns over at 9 %·d-1 (Shimamoto &
Komiya, 2000). The data presented in this thesis are the first to show that this approach is
sensitive to determine myofibrillar fractional synthesis rates (FSR) over various timeframes
simultaneously, from 3 h to 7 d (Chapter 4). Moreover, these rates were not dissimilar to values
presented elsewhere; for example, postprandial FSRs following functional testing in Chapter 4
were (0.101 ± 0.056 %· h-1; mean ± SD), which although are qualitatively higher than been
reported over similar timeframes following nutrition (0.088 ± 0.024%·h-1) (Wilkinson et al.,
2015) or nutrition with exercise (0.082 ± 0.016 %·h-1) (Davies et al., 2019), are likely explained
by the prior eccentric exercise. With that suggestion in mind, the daily rates measured in the
latter half of the study with PPB were 1.89 ± 0.82 %·d-1 pooled across leg, equivalent to 0.079
± 0.034 %·h-1. Moreover, similar daily rates measured following resistance exercise in healthy

205
young individuals are reported at 1.98 ± 0.41 %·d-1 (Holwerda et al., 2018), 1.67 ± 0.07 %·d-1
(Damas et al., 2016b) and 1.97 ± 0.37 %·d-1 (Wilkinson et al., 2014) in previously published
work, and 2.01 ± 0.69 %· d-1 in Chapter 5 over 48 h following exercise. Together, these chapters
show that the novel deuterium dosing strategy is sensitive to detect changes in MyoPS induced
by feeding and eccentric exercise, agreeing with previous work. However, the rationale for
creating this protocol was due to the absence of an isotopic steady state of body water
enrichment in previously published data, which likely influences the validity and/or sensitivity
of the measurement. Therefore, it was expected that this approach would induce less variation
due to stability in the precursor pool. Notably, the greater standard deviation in the present data
compared to that presented elsewhere suggests that this approach may not be suitable; whether
this is due to precursor pool kinetics, or variability induced by the present experimental
protocols or analytical procedures warrants further work directly comparing the two dosing
protocols.
6.2
Protein-polyphenol intervention influences muscle function
In Chapters 4 and 5, PPB accelerated recovery of muscle function after muscle damage and
improved function over 10 sessions of RET, versus carbohydrate placebo. Interestingly,
however, PPB did not support the recovery of peak isokinetic torque (Chapter 4), nor did it
support improvement in peak isometric torque with training (Chapter 5). This discordance
between measurements may be reflective of the physiology underpinning of these movements.
Indeed, a large component of maximal torque production is muscle activation, as measured by
electromyographical activity (EMG), with improvements in peak torque following the onset of
RET largely explained by greater EMG (Hakkinen et al., 1998). Moreover, these changes
precede those of muscle CSA, suggesting that early MVC improvements are largely neural

206
(Seynnes et al., 2007). Certainly, infrequent MVC testing can induce strength gains of ~14%
in the absence of additional training (Brook et al., 2015), and may abolish differences in
strength that would otherwise be expected following high or low load resistance exercise
training (Morton et al., 2016; Schoenfeld et al., 2017). Moreover, improvements in strength
occur predominantly with the practice of the specific movement (Dankel et al., 2020; Rasch,
1956), and only when strength is assessed in a manner similar to that performed during training
is an effect of protein observed (Morton et al., 2018). Strength was assessed by MVC in Chapter
5, which was measured approximately once per week in both legs (every 3 sessions). Whilst
MVCs were not performed during the training protocol, training was performed in the same
body position and the same muscle group (knee extensors). Thus, it is unlikely that participants
were naïve to the MVC measure (Rasch, 1956). Indeed, strength increased ~8%, corrected to
the control leg, in both PLA and PPB groups measured after both 10 and 30 training sessions,
indicating a clear effect of the RET protocol on MVC. Importantly, no additional effect of PPB
was observed, indicating that MVC may not be an appropriate measure to detect effects of
protein-induced improvements in strength.
Conversely, function as defined in the present thesis as total work produced over 30 isokinetic
contractions, may be more influenced by impairments in excitation-contraction (E-C) coupling
(Jones et al., 1989) or anaerobic capacity (Szczyglowski, Ade, Campbell, & Black, 2017).
Indeed, eccentric contractions appear to disproportionately reduce the force-production at low
stimulation frequencies, considered to reflect E-C coupling failure, with this reduction greater
in magnitude and duration than the loss in MVC force (Jones et al., 1989). In mice, both
contractile apparatus damage and the reduced ability to respond to an action potential following
eccentric exercise contribute to the loss of contractile force (Warren et al., 1993). As the
relationship between force and Ca2+ release is sigmoidal, reduced ability to respond to an action
potential causes a rightwards shift in this curve (MacIntosh & Rassier, 2002). Although calcium

207
handling within the muscle was not assessed in the present works, fatigue was evident as peak
torque produced during the final 5 contractions was approximately half of that produced over
the initial 5 (as demonstrated in Figure 2.2). Thus, the effects of E-C coupling failure may be
more pronounced over 30 concentric isokinetic contractions, and therefore more sensitive to
muscle damage.
Another explanation is that the function test is heavily dependent on anaerobic capacity, which
is stressed considering that the movement is isokinetic rather than isotonic in nature (i.e., the
test ends after 30 contractions regardless of fatigue, rather than ending upon falling below a
threshold to produce the required power). Indeed, 60 repeated isometric contractions performed
in a similar manner to the isokinetic test used herein is an established model to assess critical
torque (Burnley, 2009). Moreover, prior damaging eccentric exercise reduces both critical
torque and the work capacity above critical torque, the latter disproportionately more so, with
this appearing to be driven through impairments in anaerobic energy capacity rather than
central fatigue or oxygen delivery (Szczyglowski et al., 2017).
Of interest is why protein-polyphenol appears to interact with this measure. The increase in
mean fibre cross-sectional area during RET with protein, which was unrelated to increases in
myofibrillar protein synthesis, may suggest expansion in the sarcoplasmic protein pool,
particularly of proteins regulating glucose metabolism (Haun et al., 2019). Thus, it is
conceivable that the rise in function during training reflected a rise in oxidative capacity and
critical torque in Chapter 5, as is observed with 12 sessions of endurance training (Vanhatalo,
Doust, & Burnley, 2008). However, the short-term acceleration in recovery in Chapter 4
suggests that protein-polyphenol intervention may also influence anaerobic capacity, and
particularly that intervention prevented an impairment in this capacity. Regardless, should
muscle damage impair anaerobic capacity more so than critical torque and peak torque
(Szczyglowski et al., 2017), then these data might suggest that myofibrillar damage plays a

208
minor role in the drop in contractile ability. Thus, it is unsurprising that recovery is not
underpinned by myofibrillar protein synthesis. Nonetheless, it cannot be discounted that amino
acid provision supports the maintenance of E-C coupling, such as through promoting
remodelling of specific myofibrillar and/or sarcoplasmic components involved in calcium
handling, so future work is required to explore the nature by which PPB may influence the
present measures of muscle function.
6.3
An implied role of breakdown and endogenous amino acid availability
Measurements of muscle protein breakdown are technically challenging, requiring regular
sampling of arterial, venous, and/or muscle pools, as well as highly sensitive analytical
procedures to accurately model tracer kinetics (Wolfe & Chinkes, 2005). Indeed,
measurements of muscle protein breakdown were beyond the scope of this thesis and instead
MyoPS was characterised in response to exogenous protein provision and acute recovery.
Nonetheless, the present data imply a role of endogenous, intracellular amino acid availability
(i.e., derived from breakdown) that may contribute to protein synthesis, which is pertinent to
the interpretation of these findings.
Protein ingestion has been routinely demonstrated to increase rates of muscle protein synthesis
versus carbohydrate as assessed by both direct incorporation of tracer into protein and tracer
dilution within arterial, venous and intramuscular amino acid pools (Koopman et al., 2006;
Koopman et al., 2005; Miller et al., 2003; Rasmussen et al., 2000). Given that myofibrillar
proteins comprise of ~70% of total muscle protein (Vann et al., 2020), the observation in
Chapter 3 that the carbohydrate placebo stimulated rates of MyoPS to an equal extent as PPB
was unexpected (postprandial rates ~0.028 and ~0.026 %·h-1 in PLA and PPB). As discussed
in Chapter 3, the absence of a non-caloric comparison group means that the measured increase

209
compared to basal rates cannot be precluded as an artefact of the testing protocol. However,
similarities between rates of MyoPS following the feeding of protein and carbohydrate placebo
were observed again in Chapter 4 (PLA: ~0.116 %·h-1; PPB: ~0.087%·h-1), suggesting a
physiological basis to these findings. In both cases, endogenous amino acids released from
breakdown within the cell may have contributed to the measured rates of MyoPS.
Approximately ~40% of amino acids used for synthesis are derived from breakdown in fasted,
resting, healthy adults, which fluctuates in response to exercise, feeding and injury (Biolo et
al., 1995a; Biolo et al., 2002; Biolo et al., 1995b; Biolo et al., 1997). Although this notion has
not gained much attention recently, there is wider evidence of intracellular amino acids
contributing to synthesis in data presented elsewhere (Borsheim et al., 2004b; Greenhaff et al.,
2008). For example, repartitioning of amino acids used for synthesis, in favour of those derived
from breakdown, may have been observed following intravenous amino acid infusion under
the influence of varying levels of clamped hyperinsulinaemia (Greenhaff et al., 2008). As the
arterio-venous balance technique was employed, reported data reflect only amino acids that
leave and appear in the circulation from synthesis and breakdown, respectively. Indeed,
increasing insulin from basal levels significantly halved the release of amino acids from the
muscle, and as such the author concluded that insulin suppressed protein breakdown across the
leg. However, an alternative explanation is that insulin redirected amino acids from breakdown
towards synthesis, preventing them from entering the plasma pool (Biolo et al., 1995a;
Borsheim et al., 2004b; Moller-Loswick et al., 1994). Together with the (albeit statistically
insignificant) ~22% decrease of amino acid disappearance into the muscle, a fall in breakdown
rates would suggest that intracellular amino acid availability simultaneously fell. However,
rates of mixed muscle protein synthesis remained constant (~0.088%·h-1), indicating sufficient
substrate availability (Greenhaff et al., 2008). Expressed differently, these data may show that
a greater contribution of endogenous amino acids to synthesis reduces the reliance on

210
exogenous amino acids. Moreover, given that exogenous amino acid infusion rates and leg
blood flow remained constant in all conditions, the significant decrease in phenylalanine
release and possible reduction in uptake at 30 mU·L-1 insulin may suggest that endogenous
amino acid contribution to muscle protein synthesis is readily manipulated, and as a result less
reliant on exogenous availability.
That the contribution of endogenous amino acids to synthesis changes during different
physiological conditions is consistent with data presented in Chapters 3 and 4, whereby PPB
did not influence rates of MyoPS versus carbohydrate. However, interestingly, PPB stimulated
MPS by ~33% compared to PLA in Chapter 5 and appears to be the only study in this thesis
agreeing with the overwhelming evidence base suggesting that protein stimulates MPS versus
carbohydrate (for example: Borsheim et al. (2004b); Borsheim, Aarsland, and Wolfe (2004a);
Koopman et al. (2005); Koopman et al. (2006); Tang et al. (2007)). Nonetheless, Chapters 3
and 4 may represent extremes within a normal physiological spectrum (represented
schematically in Figure 6.1). That is, Chapter 3 may reflect a scenario whereby amino acid
requirements are relatively low given the experiment was performed at rest, and thus demand,
at least for the synthesis of the myofibrillar portion, can be achieved through endogenous
means. Indeed, many studies identify a greater protein synthetic response with protein feeding
over carbohydrate alone following muscle contraction (Koopman et al., 2006; Koopman et al.,
2005; Miller et al., 2003; Tang et al., 2007), but not rest (Tang et al., 2007). Furthermore, recent
evidence has emerged that synthesis of myofibrillar proteins increases with carbohydrate
consumption both at rest and after exercise in older males (Agergaard et al. (2017); Reitelseder
et al. (2019); discussed further in Chapter 3). Thus, whether stimulation of the myofibrillar
subfraction is more sensitive to endogenous amino acid availability, or whether factors relating
to feeding per se, such as GLP-1, can stimulate rates of MyoPS, highlights a focus for further
research.
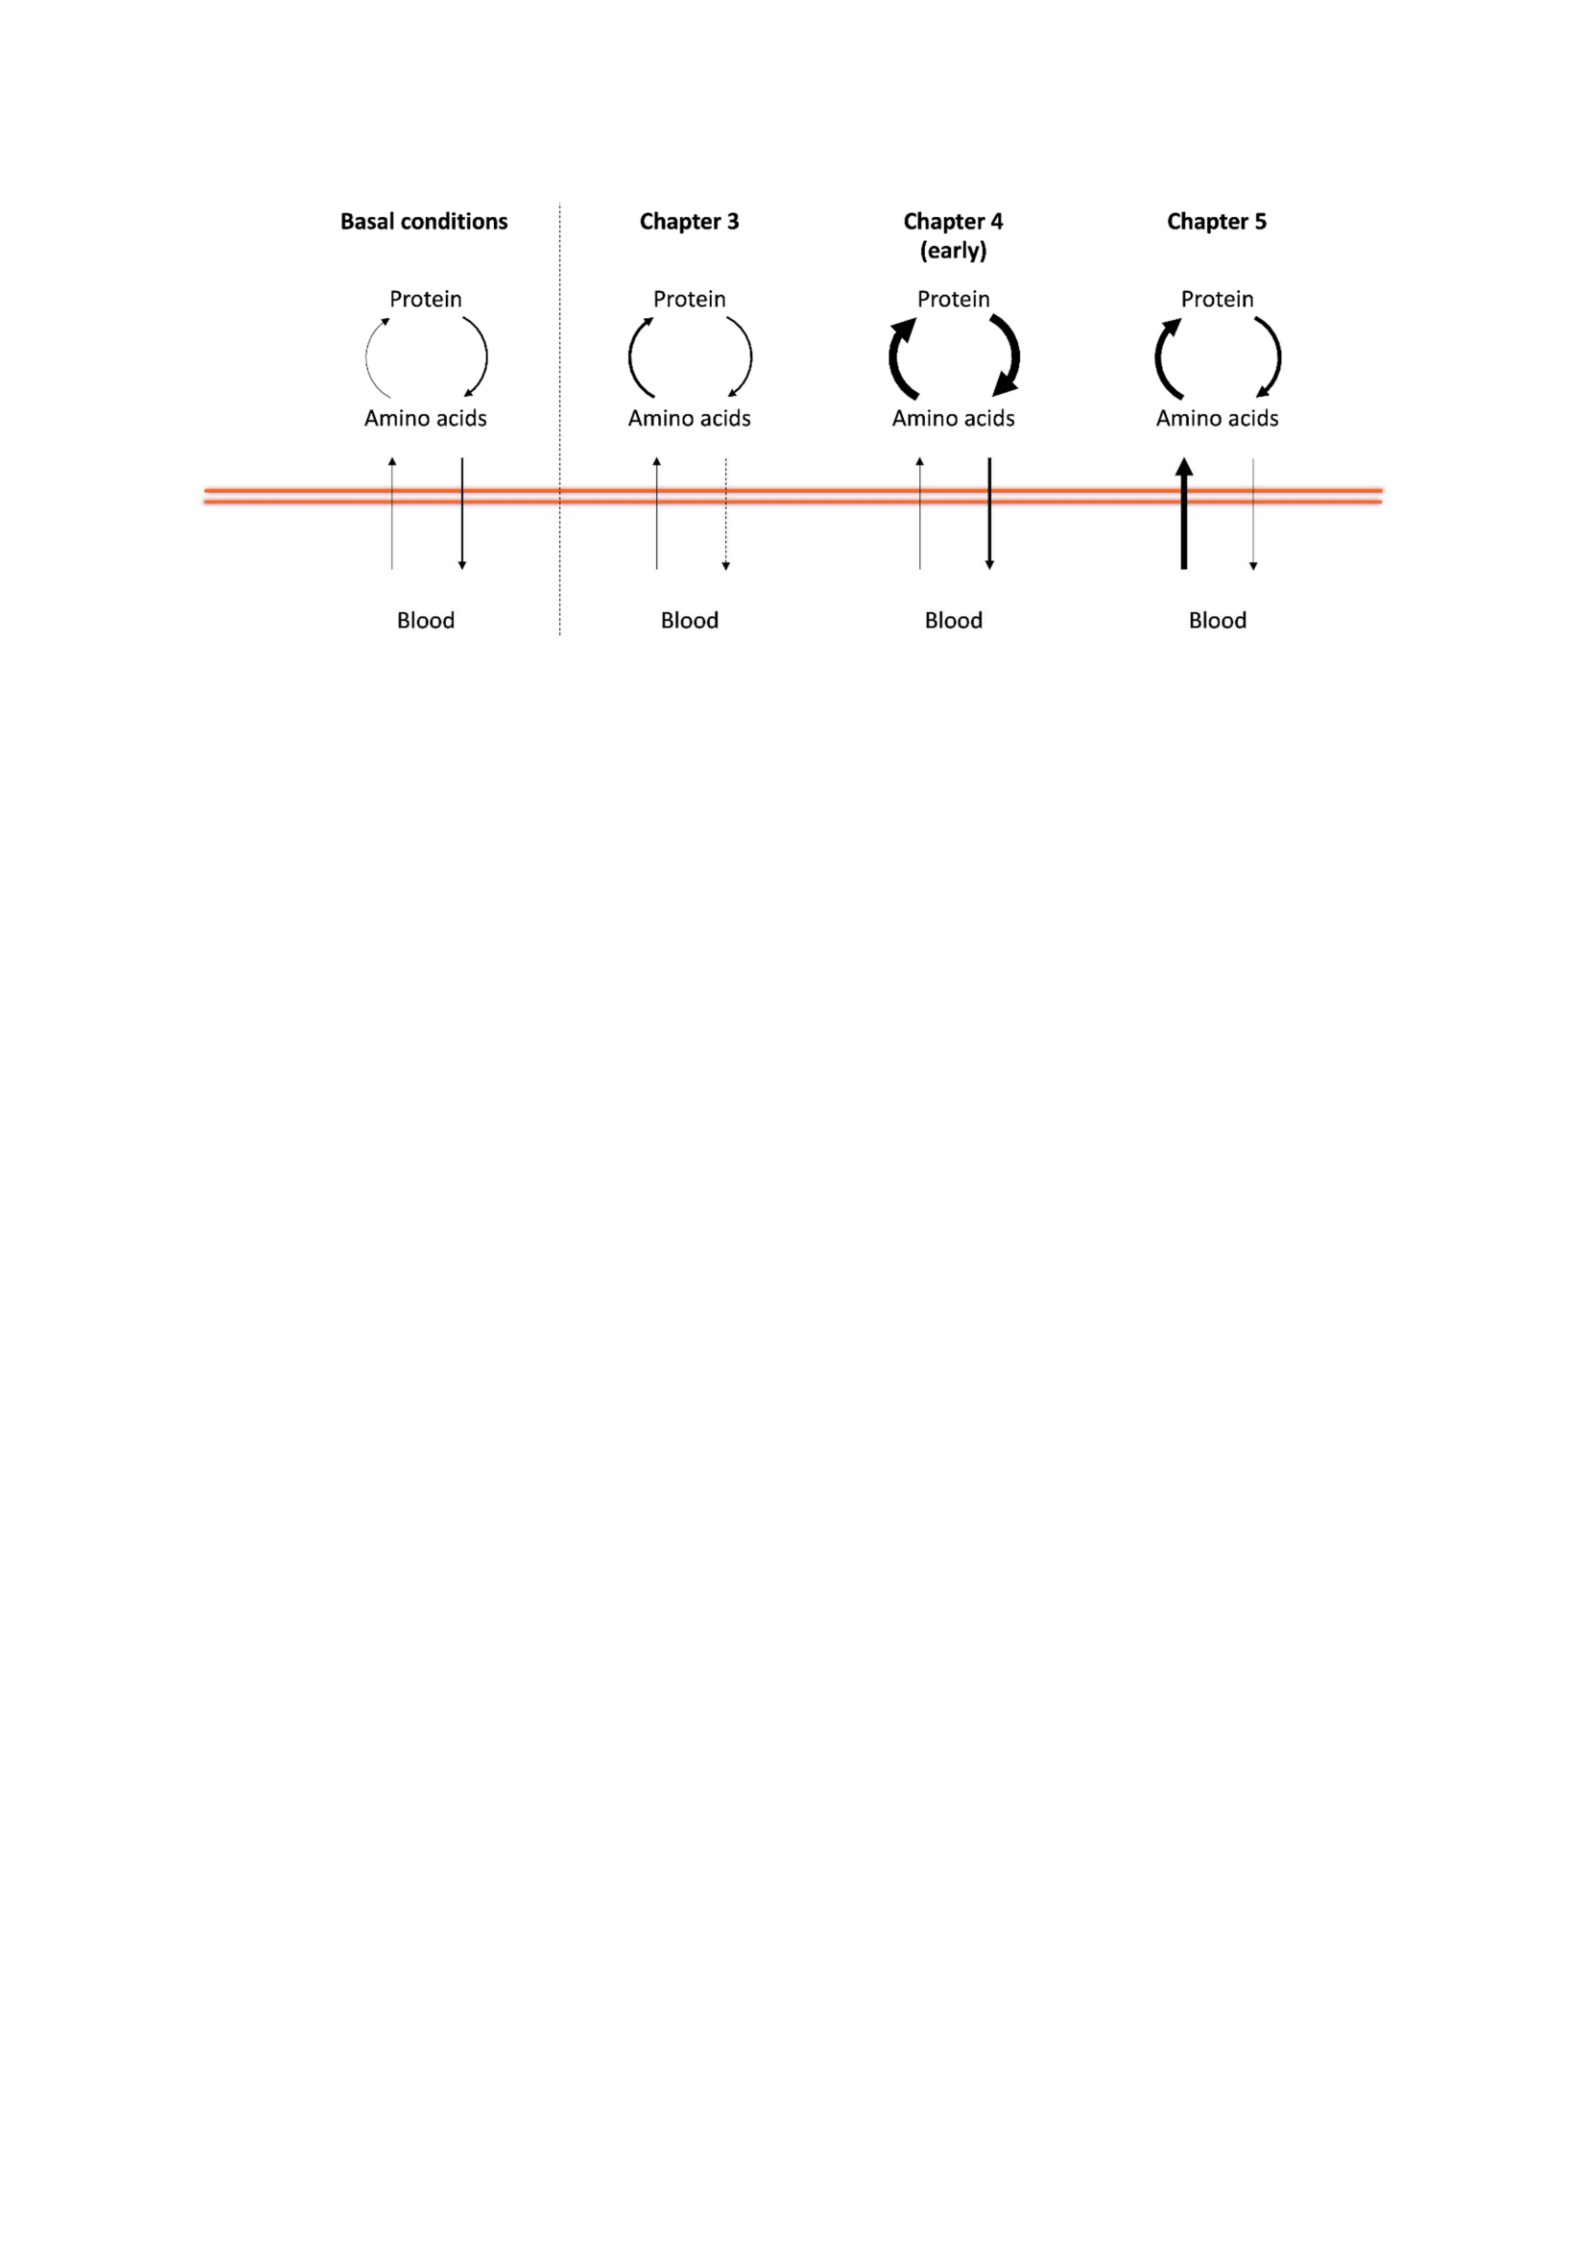
211
Figure 6.1. Schematic of possible amino acid kinetics at basal conditions and following the
experimental protocols in Chapters 3, 4 and 5. The potential of PPB to stimulate myofibrillar
protein synthesis rates is dependent on muscle uptake rates and demand for amino acids for
synthesis. Although only rates of myofibrillar protein synthesis were quantified in the current
thesis, the present data and schematic above are consistent with 3-pool modelling of amino
acid kinetics at rest, after feeding, after resistance exercise and after burn injury (Biolo et al.,
1995a; Biolo et al., 2002; Biolo et al., 1995b; Biolo et al., 1997).
Due to the comparatively high rates of MyoPS measured in Chapter 4 versus Chapter 3 (~0.10
%·h-1 over the 3 h postprandial period, versus ~0.03 %·h-1) and Chapter 5 (~2.1 %·d-1 between
24 and 72 h after eccentric exercise, versus ~1.5 %·d-1 at rest with PLA consumption), amino
acid requirements for protein synthesis were presumably high following muscle contraction.
The muscle protein breakdown response in Chapter 4 can only be inferred from existing data,
but nonetheless, the large volume of eccentric contractions may have induced a prominent
upregulation in myofibrillar and/or muscle protein breakdown creating a large supply of
endogenous amino acids to both control and damaged legs. Certainly, moderate resistance
exercise does increase rates of muscle protein breakdown between 31-50% (Biolo et al., 1995b;
Phillips et al., 1997), and severe eccentric exercise in mice upregulates rates of tyrosine release

212
from the muscle, indicative of protein breakdown, by ~60% (Lowe et al., 1995), persisting
throughout the duration of injury (> 6 days). Thus, it stands to reason that a pronounced
upregulation in muscle protein breakdown would be present following eccentric exercise and
that these endogenous proteins were used for synthesis. Further supporting this suggestion is
that despite more than 3-fold greater amino acid delivery to the muscle in burn patients versus
healthy controls, uptake from circulation provides a significantly lower proportion of amino
acids used for synthesis (~53%, versus 62% in control patients) with the remainder derived
from breakdown (Biolo et al., 2002). Moreover, in these instances, protein ingestion does not
stimulate rates of protein synthesis (Patterson, Nguyen, Pierre, Herndon, & Wolfe, 1997; Porter
et al., 2013), likely due to the already large endogenous availability (Biolo et al., 2002). In
Chapter 4, it seems likely that amino acid demand, both in the control leg and damaged leg,
was met through protein breakdown. Moreover, the observation that MyoPS fell between 72-
168 h in the PLA group despite no change in daily exogenous amino acid availability might
suggest that breakdown was attenuated after ~72 h, thereby reducing the availability of
endogenous amino acids. Although differences in the regulation of breakdown between groups
cannot be discounted, providing extra exogenous amino acids might explain why PPB
increased MyoPS only hereafter.
The response of breakdown and subsequent net protein balance in the experimental models
investigated herein require further attention, given the growing evidence base supporting the
consumption of protein or amino acids to support recovery and promote hypertrophy (as
reviewed in Chapter 1). Furthermore, support for the mechanisms described above derives from
data obtained over relatively short time frames, from ~45 mins to several hours and so may not
capture daily fluctuations in protein metabolism. Although longer-term, deuterium oxide-
derived measures of MyoPS may account for variation in synthesis, the effect on breakdown
and resultant net balance cannot be determined simultaneously. Even ignoring the possible

213
influence of hourly fluctuations in protein turnover, Chapter 4 demonstrated that cumulative
daily rates of MyoPS (and possibly breakdown) drop between 72-168 h after eccentric exercise
from those measured between 24 – 72 h, as had been demonstrated elsewhere (Wilkinson et
al., 2014). Thus, the beneficial effects of exogenous amino acids on acute recovery may be
better reflected by net protein balance over this time. Indeed, hypertrophy is a result of
sustained positive protein balance, but it remains unknown whether net balance following the
onset of training better predicts resultant adaptations. Nonetheless, the data and discussions
presented herein provide evidence that rates of MyoPS do not solely underpin these outcomes.
Further experimental evidence is required characterising the time course of protein breakdown
and net balance to delineate the relationship between protein feeding and functional outcomes.
6.4
Gene pathway analysis
In Chapter 4, the expression of 224 gene transcripts were analysed and explored using pathway
enrichment tools. These genes were selected for their roles in protein synthesis, breakdown,
insulin signalling, inflammation, myogenesis and substrate transport and metabolism, based on
previous data implicating these processes as being pertinent to recovery. The analysis plan was
decided a priori, such that all genes would be analysed for significant changes using two-way
ANOVA and then corrected for multiple comparisons using false discovery rate of <5% due to
the large number of genes being analysed simultaneously (Benjamini & Hochberg, 1995). Gene
pathway enrichment analysis was performed as an exploratory tool to determine whether any
signalling pathways were statistically overrepresented in the lists of significantly expressed
genes, which would provide insight into any biological functions that may be relevant to
recovery. Indeed, this approach identified pathways pertinent to inflammatory and regenerative
signalling over both 24 – 36 h and 24 – 168 h after eccentric exercise, but no differences were

214
observed between groups. Nonetheless, 66% and 62% of unique genes identified as being
significantly expressed (P < 0.05) were omitted from these timeframes, respectively, due to the
necessity to control for type I error (see Appendix 4 for the full list of genes with associated P-
value). Whilst this was an appropriate correction for the approach employed, the large number
of transcripts investigated provide a useful tool for future hypothesis generation. For example,
as discussed in Chapter 4, the list of omitted genes included CCL8, which was suppressed
~72% with PPB at 24 h suggesting a possible reduction in monocyte infiltration following
eccentric exercise. Additional targets indicative of a differential inflammatory response were
also observed, including IL1RL1, which was expressed 20-fold more so in the eccentrically
exercise leg than control between 24 – 36 h in PLA, versus 3-fold for the same comparison in
PPB, and IL1B, which was ~68% lower across 168 h with PPB. This may reflect specific
manipulation of inflammatory pathways with PPB, rather than wholesale changes that would
be detected by enrichment analysis. Another gene omitted was ACTN3, coding for the type II
fibre Z-disc component α-actinin-3 (North & Beggs, 1996). Expression was 2-fold greater with
PPB between 24 – 36 h after eccentric exercise. Indeed, Z-disc disruption is considered
reflective of myofibrillar turnover following muscle damage and is characterised by a notable
loss of α-actinin in disrupted Z-discs (Yu et al., 2004). Furthermore, greater rates of α-actinin
turnover are observed in sedentary males undertaking 9 days of RET (Camera, Burniston,
Pogson, Smiles, & Hawley, 2017). Therefore, expression of ACTN3 may be indicative of
greater α-actinin resynthesis. That α-actinin synthesis is enhanced by PPB and is associated
with functional improvements is consistent with the increase in type II fibre hypertrophy and
acceleration of muscle function with PPB observed in Chapter 5. These data also show an
increase in synthesis of the myofibrillar protein subfraction with PPB and a possible link
between these variables. However, MyoPS did not explain recovery in Chapter 4, suggesting
discordance in the specific myofibrillar proteins synthesised between Chapters 4 and 5, likely

215
arising due to the different experimental models employed. Therefore, while the enrichment
analysis did not reveal any pathways that may explain recovery, this approach is demonstrably
useful for further hypothesis generation.
6.5
Development of practical recommendations
The work contained within this thesis was designed to address the research questions from a
mechanistic standpoint. For example, unilateral exercise was employed to explore, and to
reduce heterogeneity in, the functional and metabolic responses to both muscle damage and
resistance exercise training, yet is performed in very few exercise scenarios. Moreover, a
combined protein-polyphenol beverage was used as a device to manipulate rates of MyoPS,
rather than to explore the roles of these individual components in recovery or training
adaptation. Whilst these methods are appropriate for the research questions posed, further work
is required to develop the findings and concepts in an applied setting before practical
recommendations can be made.
Chapter 4 suggests that in situations where exercise induced muscle damage occurs, a protein
polyphenol beverage may be an appropriate strategy to aid recovery of muscle function and
reduce soreness in recreationally active individuals. Indeed, this finding is in agreement with
recently published reviews, which tend to favour effects of protein (Davies et al., 2018;
Pasiakos et al., 2014) or polyphenols (Ammar et al., 2018; Bowtell & Kelly, 2019) individually
on recovery from resistance exercise and/or muscle damage. Although not the focus of this
present study, injury may be accompanied by a period of immobilisation, which in itself may
increase inflammatory markers such as serum TNF-α and IL-6 concentrations (Jurdana et al.,
2015). Indeed, we observed evidence of increased inflammatory signalling following eccentric
exercise, thus it is feasible that immobilisation may exacerbate the inflammatory response and

216
could delay recovery allowing for PPB to have a greater effect on recovery. Alternatively,
given that PPB did not suppress these inflammatory pathways and that immobilisation may
impair muscle protein metabolism (Drummond et al., 2012; Ferrando, Lane, Stuart, Davis-
Street, & Wolfe, 1996), the addition of immobilisation could negate the benefits of PPB on
recovery. To date, no studies have investigated the effect of a nutritional intervention when
muscle damage is accompanied by immobilisation. Thus, further work is required to explore
the scenarios in which PPB may support recovery in order for practical recommendations to be
made.
In Chapter 5, a protein polyphenol beverage was observed to accelerate functional adaptations
over ~3 weeks of RET and support type II fibre hypertrophy in previously untrained but active
individuals. This latter finding may be of relevance to individuals training for hypertrophy,
although it is unclear from these findings whether PPB would support similar fibre type growth
in already trained individuals. Meta-analysis of existing data suggests that protein ingestion
has a greater benefit on fat free mass gains in individuals who are already trained, although
fCSA is unaffected (Morton et al., 2018). Thus, it would appear that the present findings are
only applicable to previously untrained individuals. Nonetheless, whether polyphenol co-
ingestion may modulate this effect such that trained individuals may experience additional type
II fibre growth is unknown.
6.6
Limitations
The key limitation of the studies in this thesis was that only the synthesis rate of myofibrillar
proteins within skeletal muscle was measured, and thus conclusions can only be made on the
synthetic response of this subfraction. Although myofibrillar proteins are specifically damaged
following exercise (Friden et al., 1983), and resistance-trained individuals possess a greater

217
proportion of myofibrillar protein compared to untrained counterparts (Vann et al., 2020), these
data may not reflect the full muscle protein anabolic response to the interventions applied
herein. For example, as discussed in Chapter 5, sarcoplasmic hypertrophy and increased
content of glycolytic proteins have been observed following 6 weeks of high-volume resistance
exercise training (Haun et al., 2019). Whist the role of net balance and protein breakdown is
implied, as discussed above, synthesis of sarcoplasmic and/or mixed muscle protein may
provide further insight into the mechanisms dictating recovery and hypertrophy. However, a
comprehensive assessment would require larger muscle biopsy samples than were obtained,
and myofibrillar protein synthesis was relevant to the hypotheses of this thesis. An alternate
approach, albeit one that requires development in our laboratory, would be to measure turnover
rates of specific proteins using targeted proteomics (Camera et al., 2017). For example, the
synthesis rates of specific proteins within the myofibrillar subfraction may explain why PPB
influenced muscle function only. Muscle damage may result in rapid clearance of α-actinin,
and the synthesis of desmin and actin during the reparative process, as discussed in Chapter 1
(Yu et al., 2004). Alternatively, the resynthesis of α-actinin-3 as discussed above may
accelerate the recovery of Z-disc structures. Certainly, exploring these avenues in future work
would reveal more about processes underpinning recovery.
A second key limitation is that the present data were obtained in healthy, young, recreationally
active individuals. Numerous factors including age (Katsanos et al., 2005; Wall et al., 2015),
injury (Biolo et al., 2002) disease (Bell et al., 2006) and training status (Phillips et al., 1999)
influence protein metabolism. From a mechanistic point of view, applying the experimental
approaches used herein to models of disease and ageing would reveal more about the roles of
myofibrillar protein synthesis than can currently be concluded, although, in the absence of any
previous work, it is necessary to characterise the response to PPB in young, healthy individuals
first.

218
Thirdly, the role of MyoPS was investigated in response to nutritional intervention. Although
conclusions about MyoPS apply to non-pathological, normophysiologic conditions, it remains
unknown whether a pharmacological intervention would influence the present findings. For
example, following severe burns, 2.5 g·d-1 metformin in adults (Gore, Wolf, Sanford, Herndon,
& Wolfe, 2005) and ~4.9 mg·d-1 oxandrolone in children (Hart et al., 2001) increases muscle
protein synthesis rates by ~25% and ~140%, respectively, whereas exogenous amino acids
have no effect (Porter et al., 2013). Moreover, 3 mg·kg-1·wk-1 of testosterone enanthate for 12
weeks increases mixed muscle protein synthesis by ~27% in the basal state measured pre-and
post-dosing, corresponding with a ~20% gain in muscle mass (Griggs et al., 1989). When
consumed alongside strength training, androgenic-anabolic steroid use increases lean mass by
~4.5 kg over 8 weeks (Hartgens et al., 2001). Thus, pharmacologically upregulating MyoPS
may accelerate recovery from damaging exercise and promote further adaptations to resistance
exercise training. Although ethically problematic, an investigation is warranted to further
explore the role of MyoPS in recovery and training adaptation.
6.7
Conclusions
The studies contained herein combined detailed measures of myofibrillar protein synthesis and
gene expression with powerful unilateral models of muscle damage and resistance-type
exercise training, providing intra-individual, time-matched control at each data point to reduce
heterogeneity in outcomes. By detailing the time-course of recovery and prolonged training,
these data show for the first time that accelerated recovery from muscle damage with a protein-
polyphenol nutritional intervention is not explained by myofibrillar protein synthesis or a
dampening of inflammation. An additional novel finding was that only once muscle damage is
resolved
does
protein-polyphenol
intervention
improve
myofibrillar
protein
synthesis.

Applying this to a model of resistance-type exercise training, these data are the first to show
that protein-polyphenol intervention increases rates of myofibrillar protein synthesis measured
following the onset of training and accelerates early functional improvements and increases
type II fibre hypertrophy. Whilst adaptations are likely multifactorial, these results suggest that
myofibrillar protein synthesis can be targeted to promote these specific adaptations. Future
work investigating net protein balance and protein breakdown is called for to provide additional
insight into the role of protein turnover in recovery and training.

