


1
INFLUENCE OF AEROBIC EXERCISE AND LIPOLYTIC STIMULI ON PLIN3 LEVELS
IN SKELETAL MUSCLE AND ADIPOSE TISSUE IN TYPE 2 DIABETES AND PCOS
CHAPTER 1: INTRODUCTION
1.1 Type 2 diabetes, polycystic ovary syndrome, and insulin resistance
Type 2 diabetes (T2D) is a metabolic disorder characterized by insulin resistance and
hyperglycemia. In the United States, the prevalence of T2D has nearly doubled, from 3.5 per 100
people in 1990 to 8.3 per 100 people in 2012, with the incidence rate increasing from 3.2 per 1000
people per year to 7.1 per 1000 people per year [1]. In particular, the incidence and prevalence of
the disease has increased significantly in adults aged 20 to 44 over the past two decades, meaning
it now affects younger individuals compared to before.
Although the clinical criteria for diagnosing T2D are well defined, with fasting blood
glucose (FBG) ≥126 mg/dL or hemoglobin A1c (HBA1c) ≥6.5%, the exact cause of the disease
is still not fully understood. Unlike type 1 diabetes which appears suddenly at a young age, T2D
usually develops gradually and dangerously. In the early stages of the disease, the function of
pancreatic beta cells is still maintained, but hyperinsulinemia occurs to overcome insulin
resistance in body tissues.
T2D is a major disease associated with insulin resistance, but there are other conditions
that have similar characteristics. Polycystic ovary syndrome (PCOS), which affects about 4-7%
of women of childbearing age, is one of the leading causes of infertility in women. The disease is
characterized by oligo- or amenorrhea, and about 20-43% of women with PCOS experience

2
insulin resistance, as well as about 70% experience increased adiposity.
Therefore, it is important to study the pathogenesis of insulin resistance in order to
understand ways to prevent and treat this disease. The three main body tissues that have been most
studied in relation to this metabolic disorder are the liver, adipose tissue, and skeletal muscle, all
of which are insulin-affected tissues in the regulation of glucose metabolism. One of the
similarities found in individual skeletal and liver muscle biopsies with T2D is the accumulation
of excess lipids in these two tissues.
1.2 Ectopic Lipid Accumulation and Skeletal Muscle Insulin Resistance
One of the main themes that has so far prompted much investigation over the past two
decades regarding the pathogenesis of T2D is the "adipose tissue expansion hypothesis" in which
a larger amount of lipids are deposited in the skeletal muscles and liver as a result of the inability
of adipose tissue expansion (reviewed in [8]). Within the framework of this theory, the
unexplained etiology prevents adipose tissue from expanding appropriately under conditions of
positive energy equilibrium. Thus, because the excessive calorie intake of lipids cannot be
properly stored into adipose tissue, it is ectopic accumulated within other insulin-responsive
tissues.
In addition to this accumulation of ectopic lipids, skeletal muscle of individuals with T2D
has a lower lipid oxidation rate . This is coupled with the fact that insulin-resistant individuals
have lower levels of mitochondrial content for this overprocessing of lipid excess [10, 11]. Thus,
the accumulation of excess lipids is confounded by the reduced capacity to utilize them in cell
metabolism.

3
Focusing on skeletal muscle, it has been repeatedly shown that intramyocellular lipid
content (IMCL) measured by in the soleus and anterior tibialis. Nevertheless, this observation has
been confused with a phenomenon known as the athlete's paradox, in which athletes who are
highly sensitive to insulin have enormous levels of lipids in their skeletal muscles when compared
to their sedentary, but healthy counterparts. Work from our group showed that in primary skeletal
muscle cultures of physically active individuals had higher lipid levels above and above healthy
and sedentary individuals .
1.3 Lipid droplets as intracellular lipid stores
The main source of bioavailable newborn lipids stored intracellularly is in the form of lipid
droplets. Lipid droplets represent the oldest and most basic form of intracellular organelles
consisting of a phospholipid monolayer surrounding the nucleus consisting mainly of
triacylglycerides and cholesterol esters. Surrounded by a single phospholipid layer, lipid droplets
serve as lipid reservoirs needed for cellular functions whether they are metabolic, such as lipid
oxidation, or constructive, such as membrane synthesis (reviewed in [17]). Due to this relationship
with metabolism and membrane synthesis, lipid droplets have been implicated in pathological
disease states ranging from obesity and T2D to the regulation of viral replication [18-20] and
obscure inflammatory processes such as Reye's syndrome .
In 2008, Guo et al published an important manuscript highlighting the differences
Protein species are lipid droplet-related based on lipid droplet size [22]. Thus, other variations
in the protein proteome of the lipid droplet layer have been explored in relation to lipids

4
oxidation, biosynthesis of lipid droplets, trafficking of lipid droplets, and interaction with other
organelles such as mitochondria [23].
1.4 Perilipin Protein Family
The perilipin protein family represents a set of five proteins that to date have been shown
to function primarily by localizing lipid droplets. This group was originally referred to as PAT
proteins, taking the initials of the first letters of the original names of the first three: perilipin (now
PLIN1), adipocyte differentiation-related protein (ADRP, now PLIN2), and 47 kDa tail interactive
protein (TIP47, now PLIN3) [24]. Perilipin 1 (PLIN1) was first discovered in 1991 [25] and it was
shown that through an alternative splicing process it consists of four protein isoforms (labeled A,
B, C, and D), with A and B being shown to be expressed in adipose tissue and steroidogenic cells,
and with C and D being expressed exclusively in steroidogenic cells such as adrenal glands and
gonads [26]. Perhaps the most investigated is the mechanism behind intracellular signaling
between PLIN1 in adipose as a lipase-sensitive hormone (HSL) recruiter and the release of
comparative gene identification-58 (CGI-58) to adipose triglyceride (ATGL) lipose after
phosphorylation to facilitate triacylglyceride breakdown (reviewed in [27]). Importantly, however,
PLIN1 is not expressed in the skeletal muscles of mammalian species [28].
Further investigations into skeletal muscle have focused on the relationship between lipid
oxidation and other perilipines, namely perilipin 2 (PLIN2) and perilipin 5 (PLIN5), both of which
are highly expressed in skeletal muscle [28]. Investigations have shown that PLIN2 is associated
with insulin sensitivity of muscle tissue despite an increase in muscle lipids

5
accumulation [29]. PLIN2 expression is also increased in individuals with T2D after metformin
therapy [30].
The investigation of PLIN5 in skeletal muscle may have been the most widely published
and most extensive in the diabetes literature. Overexpression of PLIN5 in mice greatly increases
lipid oxidation [31], which may be partly explained by the direct protein-protein interactions
observed with ATGL [32, 33]. It was also shown that PLIN5 localized mainly in lipid droplets
containing almost exclusively triacylglycerol, while PLIN1, PLIN2, and PLIN3 localized to
droplets containing an evenly mixed mixture of triacylglycerol and cholesterol esters with
perilipin 4 (PLIN4) which localized droplets composed almost entirely of cholesterol esters [34].
PLIN5 has been shown to localize not only to lipid droplets, but also to mitochondria, which has
led to the hypothesis that PLIN5 may in some way signal mitochondrial translocation to lipid
droplets for efficient lipid oxidation [35]. Finally, PLIN5 was shown to have phosphorylation sites
on serine residues, but these phosphorylation sites were not altered by muscle contraction,
stimulation with epinephrine, or increased lipolysis [36]; this is not like the PLIN1 function.
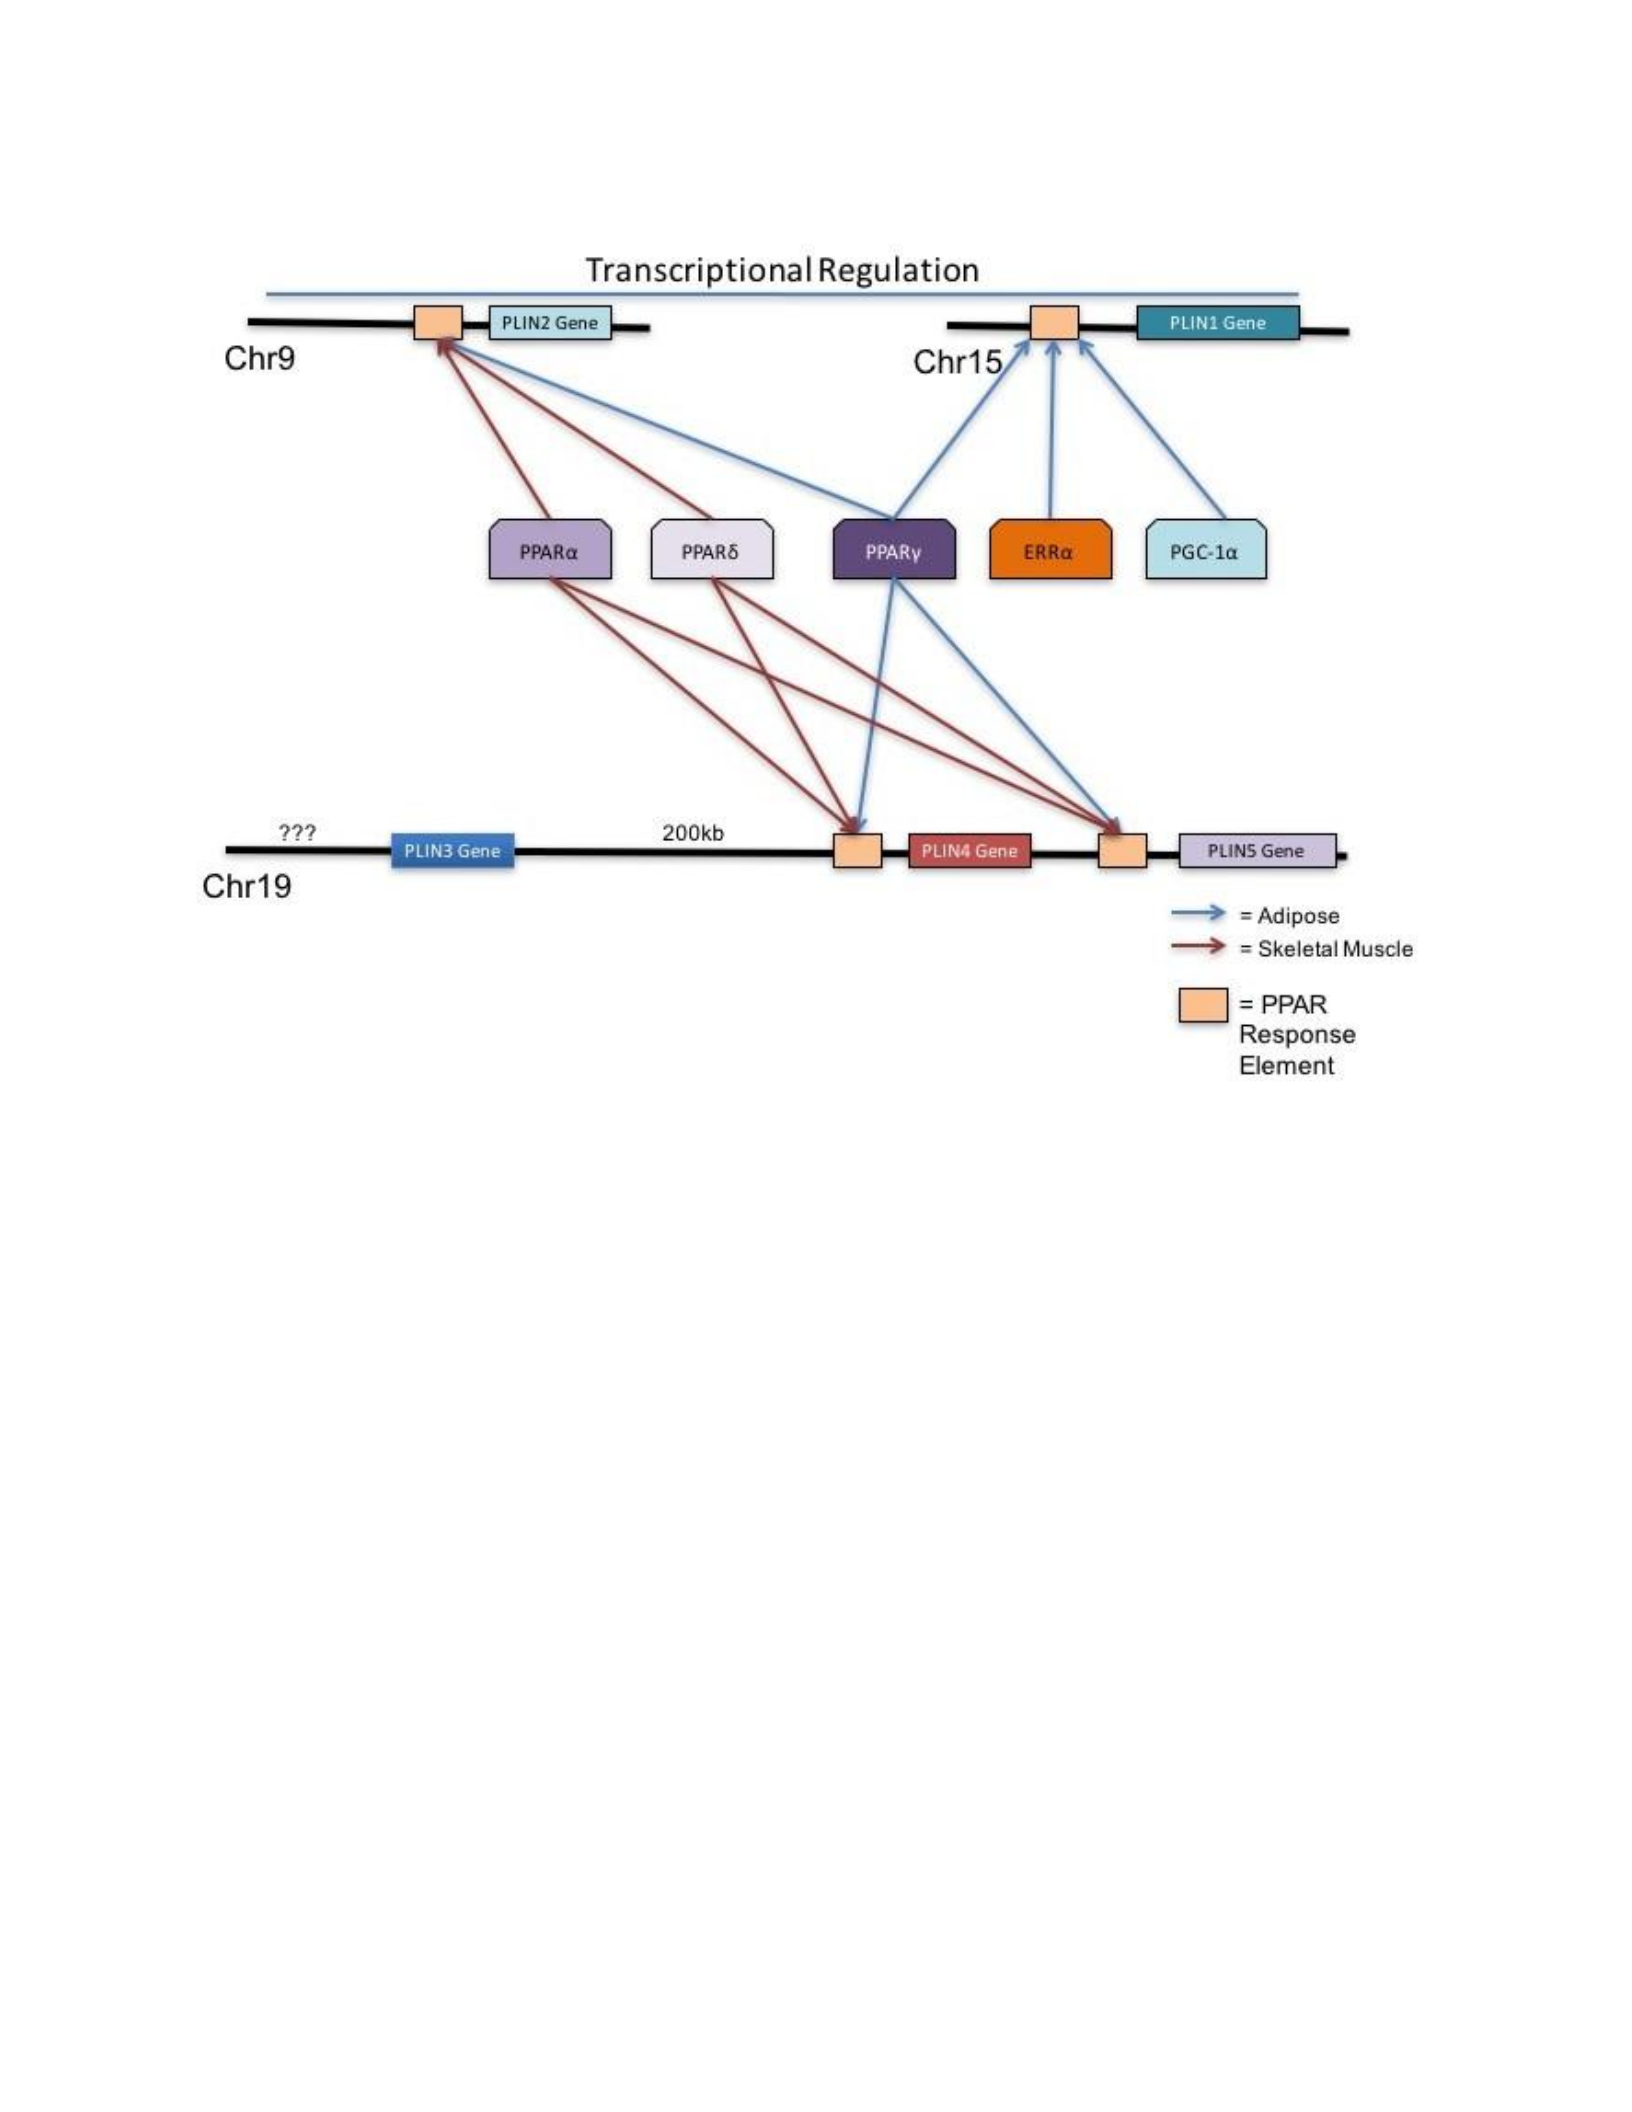
Perilipin transcription controls 1, 2, 4, and 5 have been identified in both adipose and
skeletal muscle tissue; and it has been shown that different peroxisome-activated proliferator
(PPAR) receptors and their co-factors, i.e., PPAR 1 (PGC-1 ) coactivators, appear to be
involved in their expression (Figure 1.1). Since these targets are involved in lipid metabolism as
well as adipocyte differentiation, it makes sense that lipid droplet layer proteins would be
controlled by such transcription factors. One perilipine in which the transcriptional response
element has not been confirmed is perilipin 3.
6
Figure 1.1 Current regulation of the transcription of the perilipin family through the PPAR
response element. Currently, PLIN1, 2, 4, and 5 regulation is known in both skeletal muscle and
adipose tissue. However, PLIN3 transcription regulations have not been identified. Images
constructed from the data presented in Wolins et al. [28]; Dalen et al. [37]; Targett-Adams et al.
[38]; Actor et al. [39]; Arimura et al. [40]; Dalen et al. [41]. PPAR, a peroxisome-activated proliferator
receptor; ERR, estrogen-related receptors; PGC, PPAR gamma coactivator

7
1.5 Perilipin 3
Perilipin 3 (PLIN3) is a 47kDa protein that has been described in detail through x-ray
crystallography analysis by Hickenbottom et al. in 2004 [42]. Officially named mannose-6-
phosphate receptor binding protein 1 (M6PRBP1) and tail interaction protein 47kDa (TIP47), it
has been investigated extensively as a cellular trafficking molecule involved in the transport of
mannose-6-phosphate receptors between endosomes and the Golgi apparatus, whose role
currently remains outside the scope of this investigation. Its role as lipid droplet layer protein
began to spark academic interest in relation to metabolism after the publication of Wolins et al.
[28] when it was shown to be highly expressed in skeletal muscle along with PLIN2 and PLIN5.
Previous evidence suggests that PLIN3 may have some function with respect to lipid
oxidation. Pratts et al. showed that HSL colocalizes to PLIN3-coated lipid droplets in rat skeletal
muscle [43]. Smirnova et al. showed that ATGL colocalizes with PLIN3 [44]. Although it has been
demonstrated that there is no direct protein-protein interaction between PLIN3 and ATGL [32], it
has been shown that the interaction between the ATGL co-activator, CGI-58 [45]. In addition, a
very recent discovery has found that PLIN3 also interacts with mitochondria as shown by PLIN5
[46]. However, like PLIN5, it has recently been shown that although PLIN3 has phosphorylation
sites on serine residues, phosphorylation is not affected by epinephrine-stimulated lipolysis muscle
contractions [36].
1.6 Coatomer GTP-ase interacts with Perilipin 3

8
One important element that does not seem to be present in the literature surrounding PLIN3
in relation to lipid metabolism in skeletal muscle is its interaction with the coatomeric GTPase
involved in transport between the endoplasmic reticulum (ER) and the Golgi apparatus. Soni et al.
showed that ATGL colocalizes to PLIN3-coated lipid droplets under lipolysis stimulation in HeLa
cells, a phenomenon obliterated by treatment with brefeldin A [47]. Brefeldin A is a coatomic
inhibitor of GTPase ADP-ribosylation factor 1 (ARF1) [48].
Furthermore, when several other coatomes were knocked down, namely ARF1, Golgi-Brefeldin
Resistance factor A 1 (GBF1), and beta coatomic subunit 1 ( COP1), ATGL cannot co-localize
to PLIN3-coated lipid droplets .
1.7 Pilot Data on Perilipin 3 mRNA Expression in Diabetes
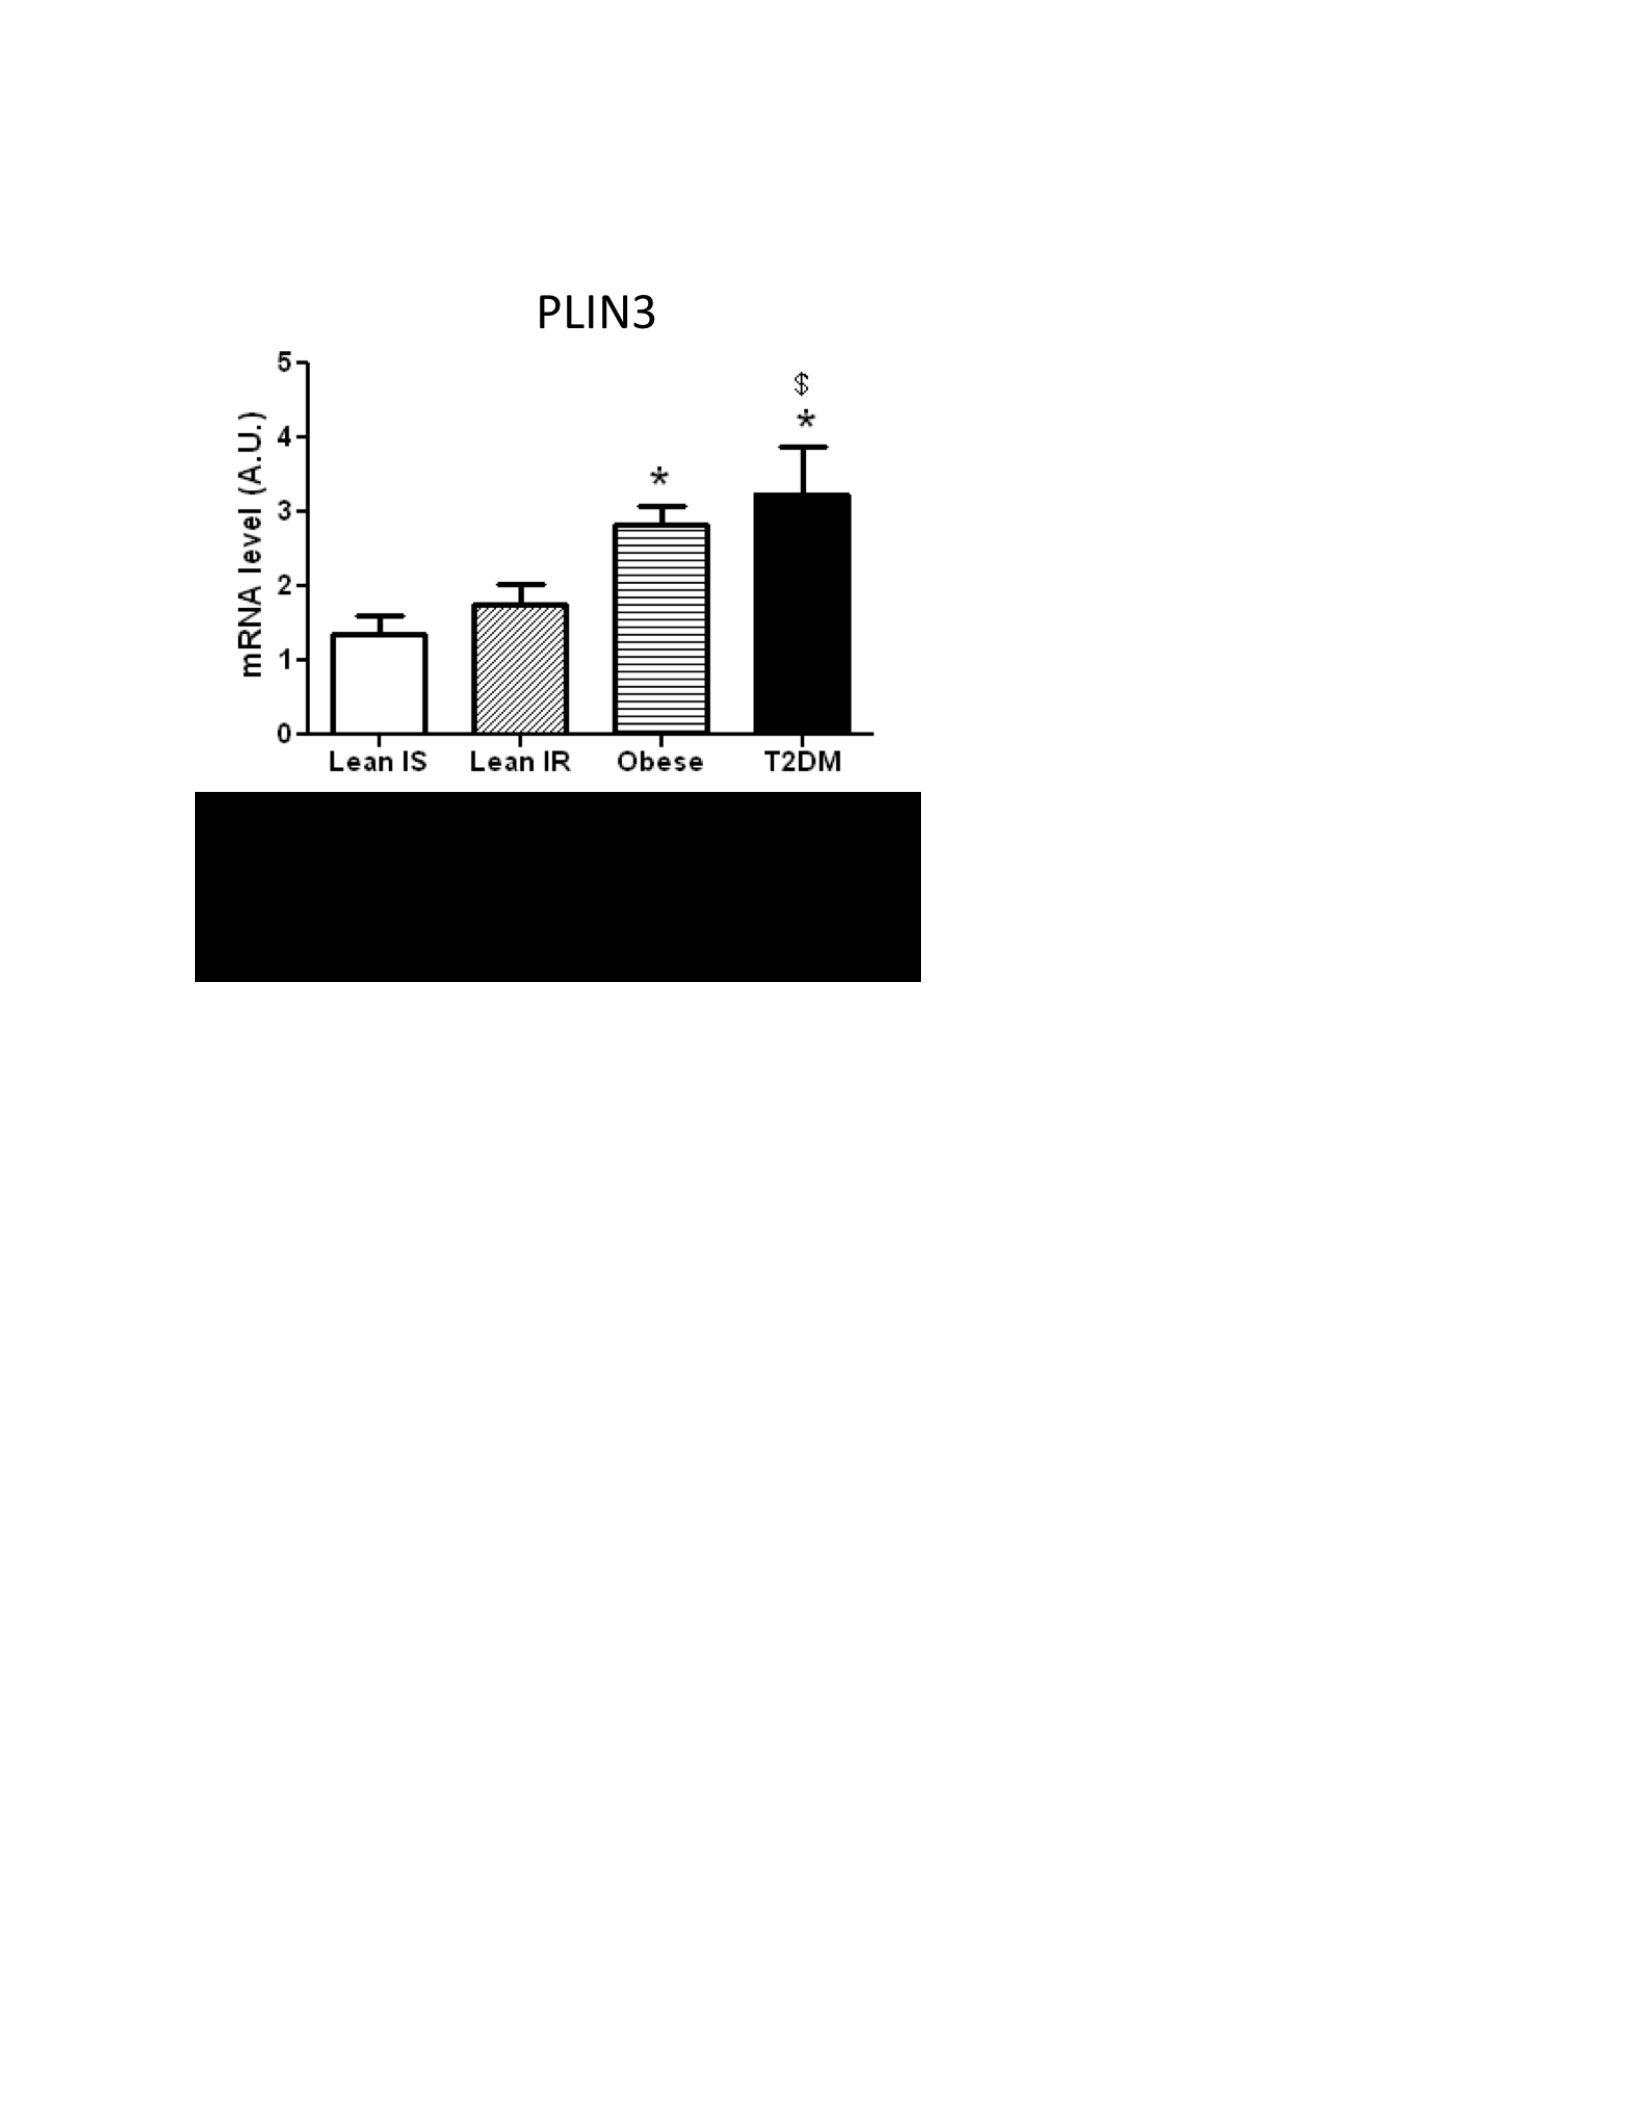
In 2008, unpublished data from our group showed a marked increase in PLIN3 mRNA
expression in skeletal muscle individuals with T2D above and above obese non-T2D individuals
and lean non-T2D individuals. This is where the initial hypothesis was formed that PLIN3 may in
some way be involved in lipid oxidation in skeletal muscle.
9
Figure 1.2: Pilot data on perilipin skeletal muscle mRNA expression 3. Individuals with T2D
have significantly higher levels of PLIN3 than insulin-sensitive individuals with a healthy weight
(thin) and insulin resistance, but no different from obese individuals.
1.8 Validity of the use of primary skeletal muscle myotubes for this investigation
Some of the experiments planned for the following investigations are dependent on the
collection, availability, and use of experiments involving primary skeletal muscle cultures that

10
are differentiated into myotubes. Using primary myotubes as well as skeletal muscle biopsy
tissues, our experiments hope to provide a more in-depth translation to understand the disease
processes associated with reduced lipid oxidation in T2D skeletal muscle. In addition, the use of
primary myotubes will allow the addition of more unethical intervention manipulation if
performed on live human study participants, such as direct pharmacological treatment of skeletal
muscle as well as institutionalizing gene knockdown via siRNA.
Thus, conducting investigations into tissues collected from human biopsies serves as a
sufficiently robust paradigm to translate back to human physiological adaptations, it is necessary
to validate that the use of primary human skeletal muscle cultures will indeed provide significant
knowledge that can be translated back into the cohort populations they represent. Previous
investigations from our laboratory have shown that lipid oxidation in myotubes retains the same
characteristics of donors [49]. Further investigations were conducted by myself and others
demonstrating the translatability of lipid content in myotubes from active, sedentary, and T2D
donors to positively reflect certain physiological characteristics such as activity level, insulin
sensitivity, and maximum mitochondrial capacity [16]. In addition, the content of primary
myotubes of ceramide and diacylglycerol species is inversely proportional to insulin sensitivity
and maximum mitochondrial capacity [16].
In continuation of this theme, it was shown in Covington et al [50] that the mitochondrial
content in the primary myotube measured by the mitochondria was positively correlated
significantly back to ex vivo expression of the mitochondrial electron transport chain complex
and in vivo measurement of the maximum mitochondrial capacity using magnetic resonance
spectroscopy.

11
Furthermore, the presence of type-I muscle fibers in culture was positively correlated with the
presence of type-I fibers in donor muscle tissue. This investigation also showed that the reflection
of these phenotypic characteristics was maintained through parts four and five of the processing
and preservation of myotube cultures. Due to the logistical fact that to utilize myotubes from so
many different biopsy sessions from so many different donors, the earliest part of the primary
myotube that can be used for investigation occurs in the fourth part. As far as our laboratory
investigations can show, it seems that the use of primary muscle cultures is, in fact, a good and
effective paradigm for providing results that can be translated back to the phenotypic
characteristics of donors for experiments that require a more mechanistic understanding.
1.9 Purpose of Investigation
The next investigation will seek to answer the following questions:
1) Does Perilipin 3 expression inhibit lipid oxidation? Thus, does lipopolitical stimulation,
either through pharmacological modifications or through increased physical activity
(i.e. resistance training), lower perilipin 3 levels?
2) In relation to perilipin 3, how do other theorized lipid oxidation markers, especially the
coatomic gtp-ases mentioned in Soni et al. [47], alter expression under lipopolitical
stimulation either through pharmacological modification or through resistance training?
3) How does knockdown Perilipin 3 alter lipid oxidation in skeletal muscle tissue?
4) How is Perilipin 3 expressed differently in skeletal muscle among physically active
individuals, healthy-sedentary individuals, and individuals with type 2 diabetes (T2D)?
Likewise, how is the coatomeric gtp-ase expressed in these three cohorts? Furthermore,

12
what Occurs in the expression of perilipin 3 and coatomeric GTP-ase with pharmacological
lipolysis stimulation? Similarly, what happens to the expression of 5 perilipins among this cohort
under lipopolitical stimulation? What happens to lipid oxidation among these cohorts when treated
with brefeldin A, a drug that blocks the action of ARF1?
5) Does Perilipin 3 natural knockdown exist in nature, and if so, what effect does it have on lipid
oxidation? Likewise, How does exercise affect the expression of perilipin 3?
To conduct the investigation in questions 1-4, we conducted 1) an experiment on primary human
skeletal muscle myotubes from physically active healthy donors, sedentary non-T2D donors, and
donors with T2D, 2) a clinical trial involving 20 healthy non-T2D men, who had skeletal muscle
tissue biopsies taken before and immediately after a 650kcal resistance training fight in non-T2D
health participants—an experimental paradigm that was shown to improve lipolysis both in vivo
at the whole-body level and in vitro in skeletal muscle tissue, and 3) a clinical trial involving 29
healthy non-T2D male participants, who had skeletal muscle tissue biopsies taken in resting
conditions and who also underwent a 24-hour stent in the metabolic chamber. To investigate
question 5, we found that naturally occurring PLIN3 knockdown exists in the adipose tissue of
women with polycystic ovary syndrome (PCOS). We conducted a clinical trial in 8 women with
PCOS and 8 weight-matched non-PCOS control women as well as a 16-week exercise trial in 8
women with PCOS, which had adipose tissue biopsies and primary adipose tissue cultures
established before and after aerobic exercise exercise.

13
It is hypothesized that PLIN3 expression in skeletal muscle is indeed related to lipid
oxidation and that differences would exist in primary skeletal muscle myotube cultures taken from
sedentary/healthy donors, physically active donors, and donors with type 2 diabetes after lipolysis
stimulation. In addition, the investigation will seek to find out whether the expression of adipose
tissue PLIN3 is associated with lipid oxidation in non-T2D insulin-resistant women with PCOS,
and what are the effects of aerobic exercise on adipose tissue expression of PLIN3.

14
CHAPTER 2: PERILIPIN 3 SKELETAL MUSCLE AND COATOMER PROTEIN
INCREASE AFTER EXERCISE AND ARE ASSOCIATED WITH FAT OXIDATION1
2.1 Introduction
Since the discovery that intramyocellular lipids (IMCLs) are inversely correlated with
insulin sensitivity in skeletal muscle, understanding lipid metabolism in skeletal muscle has been
at the top of insulin resistance research. The dynamics of lipid droplets is integral to understanding
lipid metabolism as a whole. [12-14]. Parallel to that, it has also been shown that endurance-trained
athletes as well as individuals with type 2 diabetes both have high IMCL, while insulin sensitivity
in these two groups remains opposite, [15] thus, suggesting that simply having a high IMCL does
not necessarily result in insulin resistance. Therefore, understanding the regulation of lipid droplet
dynamics in skeletal muscle will likely be integral to understanding lipid metabolism as a whole.
Studies of the perilipin protein family have shown that perilipin 2 (PLIN2, also known as ADRP)
and perilipin 5 (PLIN5, also known as OXPAT) appear to be the basis for the oxidation of lipid
droplets and the interaction of lipid droplets with mitochondria [29, 31, 35, 51-55]. However, some
researchers have explored the regulation of perilipin 3 (PLIN3, also known as TIP47), a prominent
and highly expressed lipid droplet-related protein in skeletal muscle and its impact on lipid
oxidation [45, 55, 56].
PLIN3 co-localizes to lipid droplets on the stimulation and contraction of epinephrine in
rat skeletal muscle [43]. Likewise, adipose triglyceride lipase (ATGL), the main lipase present in
skeletal muscle, has been shown to co-localize to PLIN3-coated lipid droplets [44, 45]. Koatomer

15
GTPase may have a possible regulatory role in the delivery of ATGL to PLIN3-coated lipid
droplets via transport through the endoplasmic reticulum to the Golgi apparatus [47]. Treatment
with brefeldin A, a compound known to inhibit ER-to-Golgi transport, prevents ATGL from
localizing to PLIN3-coated lipid droplets in HeLa cells [47]. In addition, knockdown of the
ribocylation factor ADP 1 (ARF1), ARF-associated protein (ARFRP1), and the brefeldin-specific
Golgi-1 (GBF1)-resistant guanine nucleotide exchange factor in HeLa cells and brown adipose
tissue also prevented the colocalization of ATGL to PLIN3-coated lipid droplets [47, 57]. To date,
only a few studies have investigated this pathway in skeletal muscle or in relation to exercise
stimulation and therefore the availability of lipids for oxidative metabolism [45, 56]. Because
resistance training is highly dependent on lipid oxidation [58] and that athletes trained in resistance
training have high levels of IMCL [15], we hypothesize that perilipin 3 will be associated with
exercise-induced lipolysis.
Therefore, we investigated the effects of exercise on PLIN3 protein and lipid droplet-
related coatomeric using in vitro and in vivo approaches. In vitro experiments were conducted
using epinephrine [59] to stimulate lipolysis as well as a pharmacological cocktail of palmitate,
forskoline, and ionomycin (PFI) to induce lipolysis in a primary human skeletal muscle cell culture
model [60]. PLIN3 was also measured from biopsies of human skeletal muscles taken before and
after long-term resistance training. Next, we investigated the expressions of ATGL and GTPase
that are known to govern ER-to-Golgi trading. These data demonstrate the important coatomeric
role of PLIN3 and ER-to-Golgi in relation to skeletal muscle lipid metabolism, and offer insights
into potential novel lipolytic pathways for lipid metabolism in skeletal muscle.

16
2.2 Method and Materials
2.2.1 Ethical Statement
The participants gave their written consent and all aspects of the study protocol were
reviewed and approved by the Institutional Review Board at the Pennington Biomedical
Research Center.
2.2.2 Formation of Primary Human Skeletal Muscle Culture
Primary muscle cultures were formed from muscle biopsies obtained from vastus lateralis
in five lean and healthy Caucasian male donors (Age 23.0 ± 1.9 years and BMI 24.2 ± 0.6 kg/m2).
The formation of human primary muscle cultures has been modified from the protocol as described
earlier [61]. Myoblastic skeletal muscle progenitor cells were immunely sorted using 5.1H11
antibodies provided by the Hybridoma Bank (University of Iowa) and the MACS cell sorting
column system (Miltenyi Biotec, Auburn, CA). Myoblate cultures from five donors were grown
simultaneously to approximately 90% of the meeting and then pooled together for the experiment
using the protocol described earlier [62]. The cells were subsequently grown to approximately
80% of the encounters, and then treated with α-Minimum Essential Medium (Life Technologies,
Grand Island, NY) supplemented with 2% fetal serum (Life Technologies, Grand Island, NY), 1%
bovine fetuin (Sigma, St. Louis, MO), and 1% Penstrep at 5 mg/mL (Life Technologies, Grand
Island, NY) to induce differentiation. The cells are retained in a differentiation medium for 7 days
and are considered as myotubes on visual assessment of fused, longitudinal, and multinuclear
cells.

17
2.2.3 In vitro Treatment of Epinephrine and PFI with Primary Human Myotubes
Myotubes were treated using a technique adapted from Watt et al. [59] with 100 μM
Epinephrine (Sigma, St. Louis, MO) for a time course of 15 minutes, 30 minutes, and 1 hour with
total protein collection at each time point. For the PFI experiment, myotubes were treated with 30
μM palmitate, 4 μM forskoline, and 0.5 μM ionomycin (PFI) – all purchased from Sigma (St.
Louis, MO). We previously showed that PFI treatment in myotubes increased palmitate oxidation,
increased expression of mitochondrial oxidative phosphorylation complexes, and increased
glucose absorption [60]. Briefly, the myotube is maintained in a differentiation medium for 4 days
and then treated for 1 hour daily with PFI for an additional 3 days. The differentiation medium is
also changed daily, without PFI, for the control cells. After 3 days of PFI treatment, total proteins
and mRNA were collected immediately after PFI (0 minutes) and for a period of 15 minutes, 30
minutes, and 1 hour after PFI treatment. Total proteins were collected using RIPA buffer (Sigma,
St. Louis, MO) supplemented with 2% Protease Inhibitor Cocktail (Sigma, St. Louis, MO), 2%
Phosphatase Inhibitor Cocktail 2 (Sigma, St. Louis, MO), and 2% Phosphatase Inhibitor Cocktail
3 (Sigma, St. Louis, MO). Total mRNA was collected using QIAzol (Qiagen, Germantown, MD).
2.2.4 Endurance Training in Human Participants
Twenty healthy and normoglycemic male participants (16 Caucasian, 3 African-
American, 1 unspecified race) who were not involved in sports at a competitive level, were
recruited to participate in this trial. The characteristics of these participants are provided in Table
1. Body composition was assessed by dual-energy x-ray absorptiometry (DXA, QDR 4500A;
Hologics, Waltham, MA) and VO2max measured on stationary bicycle ergometers (Lode
Excalibur, Groningen, Netherlands) uses an additional workload protocol with simultaneous gas
exchange measurements using a metabolism cart (TrueOne 2400; ParvoMedics, Sandy, UT).

18
VO2max and DXA measurements were assessed at a period of more than 2 days prior to the
exercise intervention to prevent the confounding acute effects of exercise on baseline
measurements. Prior to the training exercise, participants were treated at night to the institution's
inpatient unit. The next morning, after fasting overnight, the resting metabolic rate was measured
using the DeltaTrac metabolic cart and a biopsy of the skeletal muscles of the vastus lateralis
muscle was performed. Additional results from this exercise trial have been published [63]. Gas
exchange during exercise is assessed from the expired air collected by the funnel using a
Parvomedics TrueOne 2400 metabolism cart. The total energy expenditure and oxidation of the
substrate are calculated as described earlier [64]. Participants then exercised on a stationary bike
with 50% of their VO2max until they exhaled 650 kcal.
Indirect calorimetry measurements are done after 8%, 20%, 40%, 60%, 80% and just before the
end of the exercise to measure when 650 kcal of energy has been expended. Blood is drawn
periodically coupled with indirect calorimetry measurements with epinephrine and norepinephrine
determined by chemiluminescent immunoassay (Immulite 2000™, Siemens Healthcare
Diagnostics, Deerfield, IL); serum glucose, insulin, and lipids with enzymatic assays on the
Beckman Coulter DXC 600 (Beckman Coulter, Brea, CA). The manufacturer's protocol is
followed for all serum measurements. Here we only report serum sizes from before and after
exercise (Table 2). Immediately after the training fight, a biopsy of the second percutaneous
skeletal muscle was obtained from the proximal vastus lateralis to the first biopsy.

19
2.2.5 Skeletal Muscle Biopsy Procedure
After local anesthesia with lidocaine/bupivacaine, skeletal muscle samples were collected
using the Bergstrom technique with suction from vastus lateralis (Propper Manufacturing Co.,
Long Island City, NY). Two separate incisions were made to collect tissue at the beginning and
post-training. The collection of a second biopsy was obtained within a period of no more than 3
minutes after the completion of the exercise. All skeletal muscle samples were visually assessed
and cleared for intramuscular adipose tissue, and then immediately frozen in liquid nitrogen for
mRNA and Protein measurements. The samples were dried and then installed in a mixture of
Optimum Cutting Temperature (OCT, Thermo Scientific, Waltham, MA) and Tragacanth powder
(Acros, Geel, Belgium) for immunohistochemical measurements of glycogen, intramyocellular
lipids, and fiber typing. Other samples were collected for ex vivo palmitate oxidation
measurements.
2.2.6 Immunohistochemical Action
Intramyocellular fiber and lipid typing (IMCL) measurements were performed as
described earlier using immunofluorescence techniques [63]. Fiber typing was carried out by
immunohistochemistry performed at 12 μm, obtained using Microm HM 550 (Thermo Scientific,
Waltham, MA). Mouse-specific monoclonal antibodies for type 1 slow myosin heavy chains
(MHC1) are used to detect type 1 (MAB1628; Millipore, Burlington, MA), and mouse monoclonal
antibodies against laminin (AB2500; Abcam Inc, Cambridge, MA) is used to detect myofiber cell
membranes. The sections are then stained with Bodipy 494 dye (Molecular Probes, Eugene, OR)
to be stained for IMCL. Image taken using a confocal microscope (Leica TCS SP5 AOBS
multifocal scanning resonance, Leica

20
Microsystems, Wetzlar, Germany) and type I fibers are counted. IMCL was determined using
Sigma Scan Pro 5 software (SPSS, Chicago, IL) by depicting Bodipy staining inside the
myofibers. Glycogen content was measured using Periodic Acid, Shiff staining and analyzed using
Sigma Scan Pro 5 software [65]. Representative images from before and after the exercise
intervention for IMCL, fiber typing, and glycogen are provided in additional images
2. For all histological sizes, three cross-sectional slices are obtained within the tissue. No less
than 50 fibers are graded from each cross-sectional slice for IMCL content, fiber type, and
glycogen content.
2.2.7 Ex vivo Palmitate Oxidation Action on Skeletal Muscle
Palmitate oxidation tests are performed on skeletal muscles as described earlier [63].
Briefly, about 75 mg of skeletal muscle tissue was homogenized and fed into trap plate equipment
to assess gas exchange for fatty acid oxidation. 0.176 μM total palmitate (0.088 μM [1-14C]-palmitate
in 0.088 μM non-radiolabel palmitate) was added to the muscle homogenate. Radiolabeled
palmitate is obtained from American Radiolabeled Chemicals (St. Louis, MO). Radiolabeled 14CO2
and incomplete acid-soluble intermediates from palmitate oxidation were assessed using
scintillation calculations. The data were adjusted to the total protein content obtained from muscle
homogenates determined through bicinchoninic acid assays (Pierce BCA, Thermo Scientific,
Waltham, MA).
2.2.8 Gene Expression in Skeletal Muscle
Total mRNA from in vivo and in vitro experiments was extracted using the miRNEasy
mini Kit (Qiagen, Germantown, MD), and the cDNA was created using the High Capacity cDNA
Kit (Applied Biosystems, Foster City, CA). Gene expression detection is performed

21
using TaqMan Gene Expression Assays-on-Demand (Applied Biosystems, Foster City, CA); the
catalog number list for each gene product is as follows: Ribosomal Protein, Large Protein O
(RPLPO; Hs99999902_m1); Koatomer 1, beta subunit (βCOP1; Hs00200674_m1); Koatomer 2,
subunit sec23a (Sec23a; Hs00197232_m1); ADP-Ribosylation Factor 1 (ARF1; Hs00796826_s1);
Golgi Brefelden Resistant GTPase Exchange Factor 1 (GBF1; Hs00188327_m1); ARF-related
peptide 1 (ARFRP1; Hs00182389_m1); PPARgamma, a 1-alpha co-activator (PGC1α;
Hs01016719_m1); Alpha proliferative receptor peroxisome (PPARα; Hs00947538_m1); Pyruvate
Dehydrogenase Kinase 4 (PDK4; Hs01037712_m1); and Beta-hydroxyacyl-CoA Dehydrogenase
(β-HAD; Hs00193428_m1). Real-Time QPCR was performed using the 7900HT Rapid Real-
Time PCR system (Applied Biosystems, Foster City, CA), and the expression level was
determined against the standard curve. Skeletal muscle and myotube gene expression is adjusted
to RPLPO expression.
2.2.9 Protein Content in Skeletal Muscle
Protein content was measured from total protein extracts by western immunoblotting using
Criterion equipment and 12.5% SDS-polyacrylamide gels (all purchased from Bio-Rad, Hercules,
CA) and adjusted to GAPDH (AB9484; AbCam, Cambridge, MA) or total protein assessed by
Ponceau S staining (Sigma, St. Louis, MO). Antibodies for PLIN3 were purchased from Novus
Biologicals (Cat no. NB110-40764, Littleton, CO). Antibodies for GBF1 (AB86071), ATGL
(AB109251), and ARFRP1 (AB108199) were purchased from AbCam (Cambridge, MA).
Antibodies for ARF1 were purchased from Epitomics (Cat no. 1635-1; Burlingame, CA).

22
2.2.10 Statistical Analysis
Data was analyzed using PRISM GraphPad Software, version 6.0 (GraphPad Software, La
Jolla, CA). All data were found to be distributed normally using the Shapiro-Wilk Normality test.
The paired students' two-way t-test was used to assess baseline measures and interventions, and
Pearson correlations were used in the practice intervention. One-way ANOVA is used to
determine differences in gene expression at different time points for in vitro PFI experiments.
The p-< value of 0.05 is considered statistically significant.
2.3 Result
2.3.1 Changes in PLIN3 in response to in vitro epinephrine and lipolysis cocktail (PFI treatment)
in human myotubes.
The protein content of PLIN3 increases steadily with stimulation of epinephrine over time
(Figure 2.1A). Likewise, the ER-to-Golgi GTPase coatome ARF1 and ARFRP1 also increased
(Figure 2.1A) 30 min and 1 h after epinephrine stimulation, respectively. The coatomer GTPase,
GBF1 is maximally expressed after 30 minutes of epinephrine before a marked maximum increase
in PLIN3 and ARFRP1 (Figure 2.1A). ATGL levels barely changed during the duration of
epinephrine treatment (Figure 2.1A).

23
Figure 2.1. Epinephrine and the lyopolitical cocktail (PFI) in the human primary myotubule
increase the perilipin 3 and coatomeric proteins. A) Primary human skeletal muscle myotubes
(n=5) are stimulated with 100uM epinephrine. The expression of PLIN3 as assessed by
densitometry increases continuously with epinephrine. In addition, the GTPases ARF1 and GBF1
increased 30 minutes after epinephrine stimulation and ARFRP1 increased 1 hour after
epinephrine stimulation. B) The protein content of PLIN3, ATGL ARFRP1, GBF1 and ARF1
increased after in vitro lipopolitical stimulus (PFI) in the myotube of primary human skeletal
muscle (n=5).
In response to the lipolimic cocktail (PFI), the protein content of PLIN3 increased
immediately after PFI treatment when compared to control conditions, reaching a maximum value
after 30 minutes (Figure 2.1B). Similarly, the coatomeric GTPase GBF1 has a maximum
expression that coincides with the maximum expression of PLIN3 at a 30-minute time point
(Figure 2.1B). PFI treatment increased the coatomic expression of GTPase ARFRP1 (Figure 2.1B).
Finally, ATGL expression increased, albeit slightly, over control immediately after completion of
24
PFI treatment which continued to decline up to 1 hour after PFI treatment (Figure 2.1B).
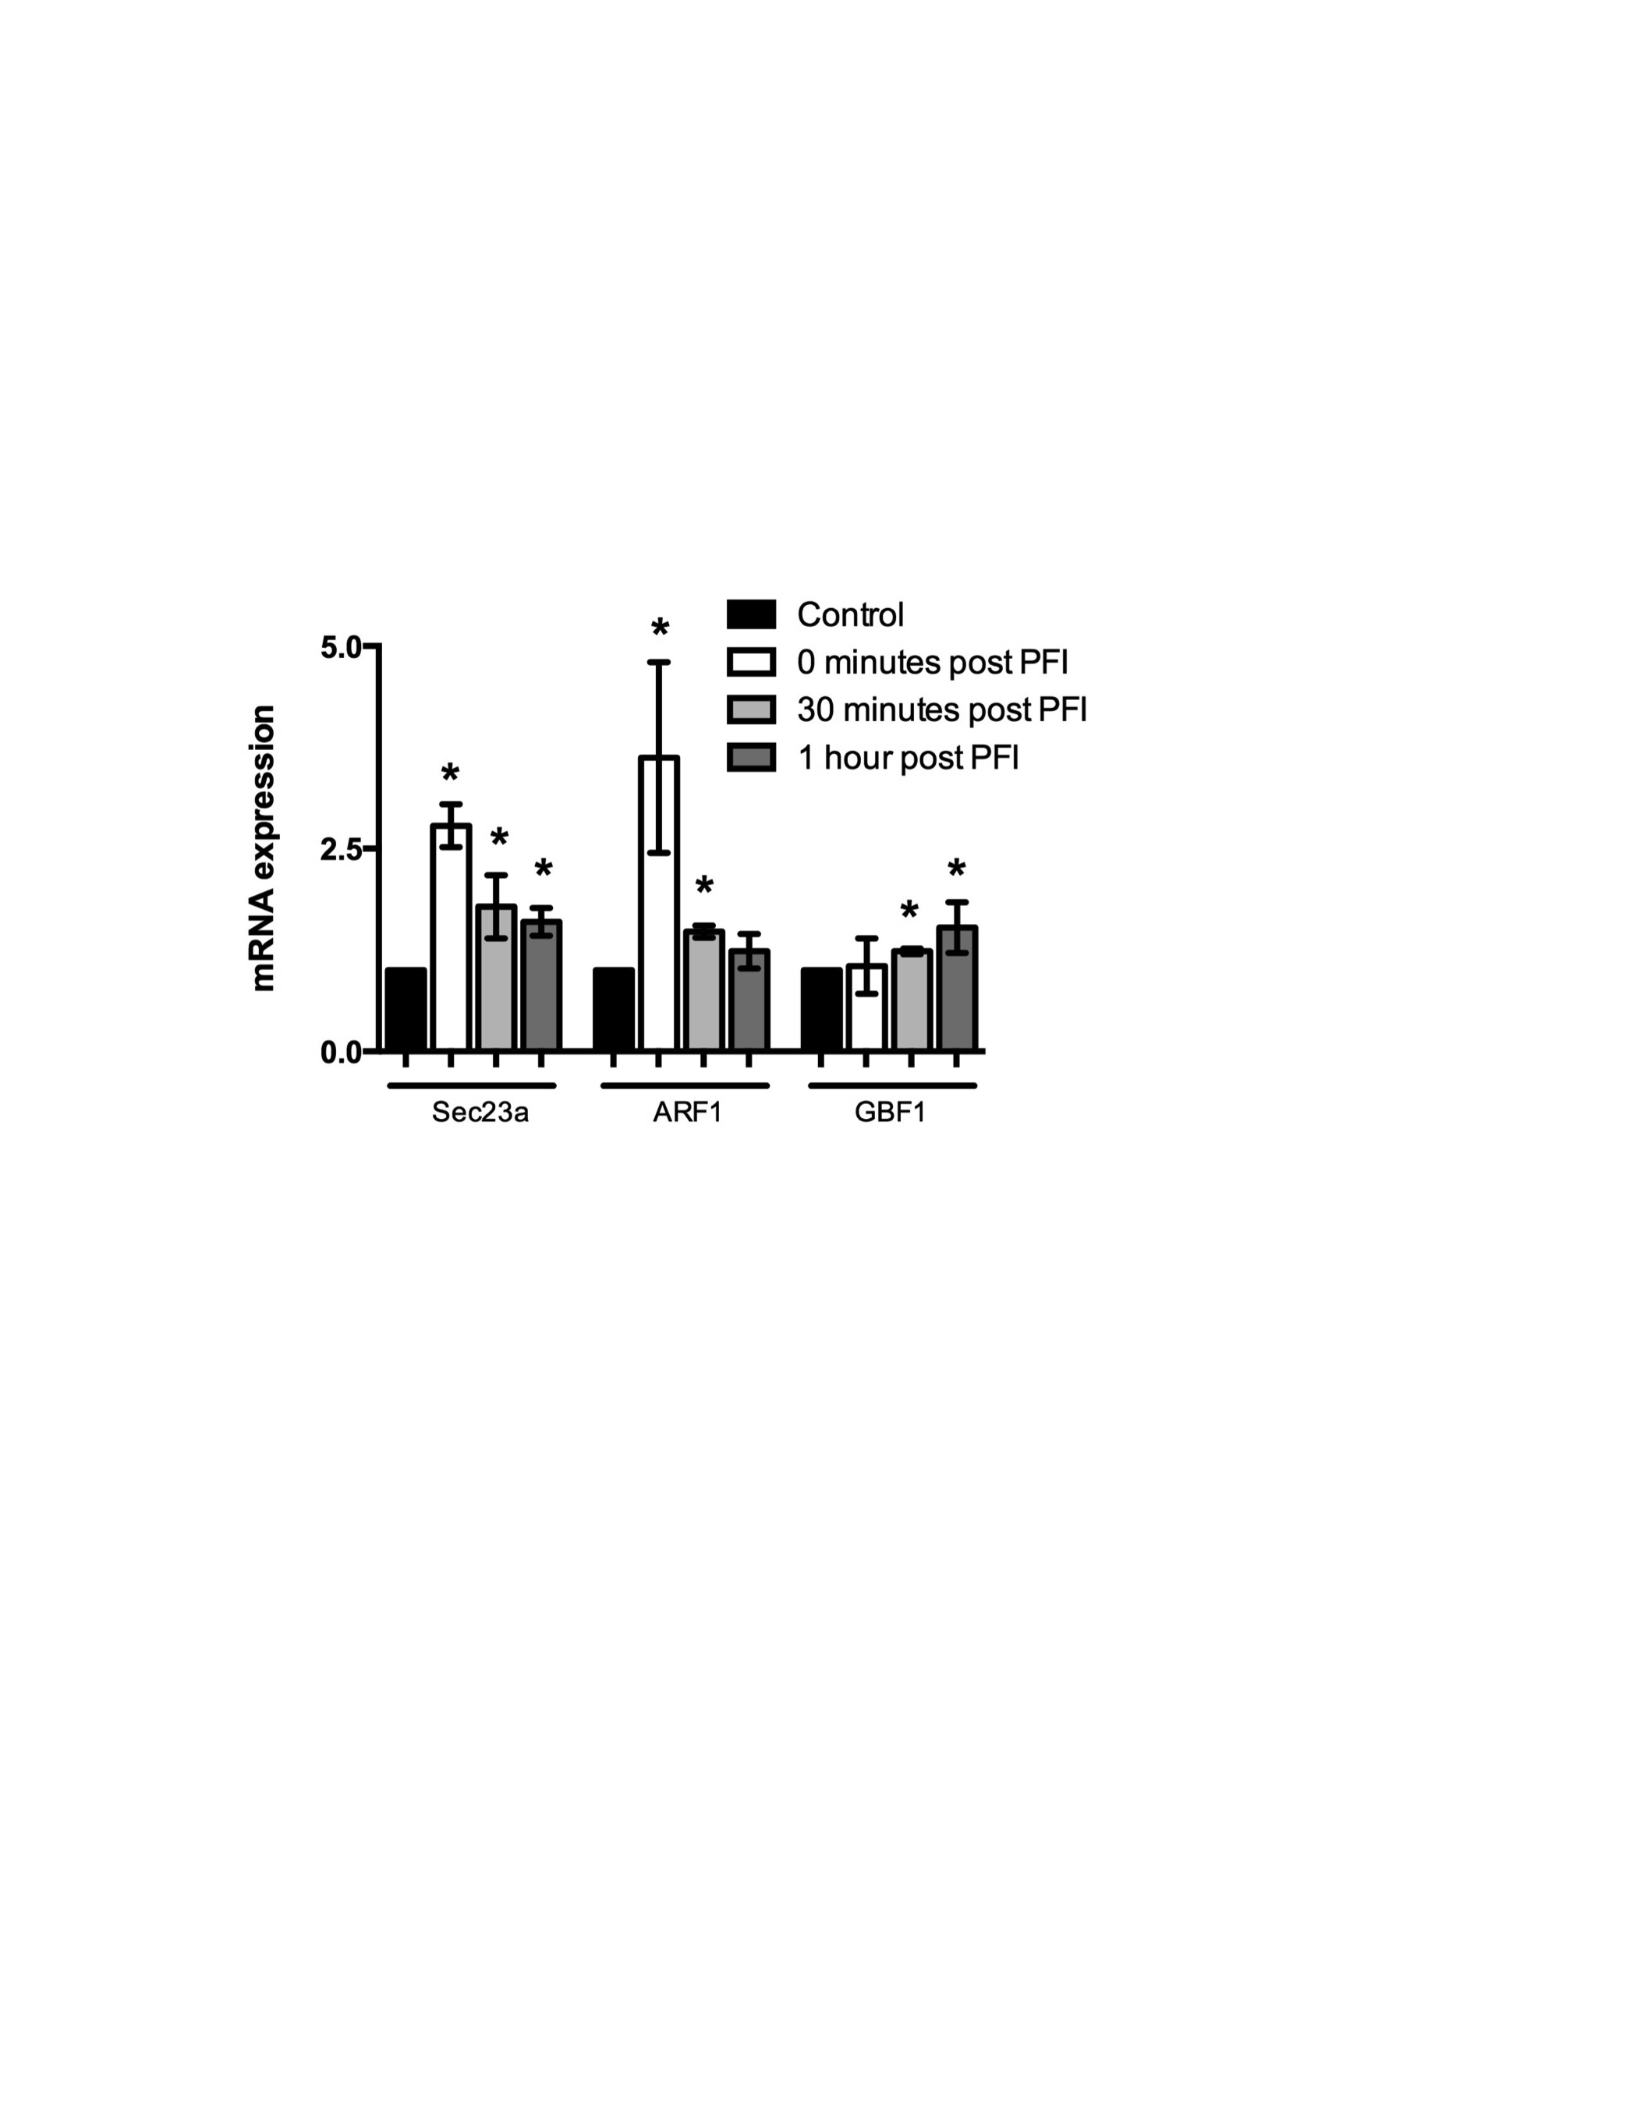
Regarding the expression levels of mRNA, sec23a, subunits of the coatomic protein
complex 2 (COPII), and arf1 increased by 2.5 and 3-fold immediately after PFI treatment,
respectively (Figure 2.2). Expression of gbf1 mRNA did not achieve a significant increase until
30 min and 1 h after PFI treatment (Figure 2.2).
Figure 2.2. The expression of the coatomic gene GTPase is altered by the lipolimic cocktail
(PFI) in the human primary myotubes. Levels of mRNA Sec23a, ARF1 and GBF1 in cultured
human myotubes before and after PFI treatment (0.30 min and 1 h) (n = 5). *p < 0.05
25
2.3.2 Changes in PLIN3 in response to resistance training in human muscles
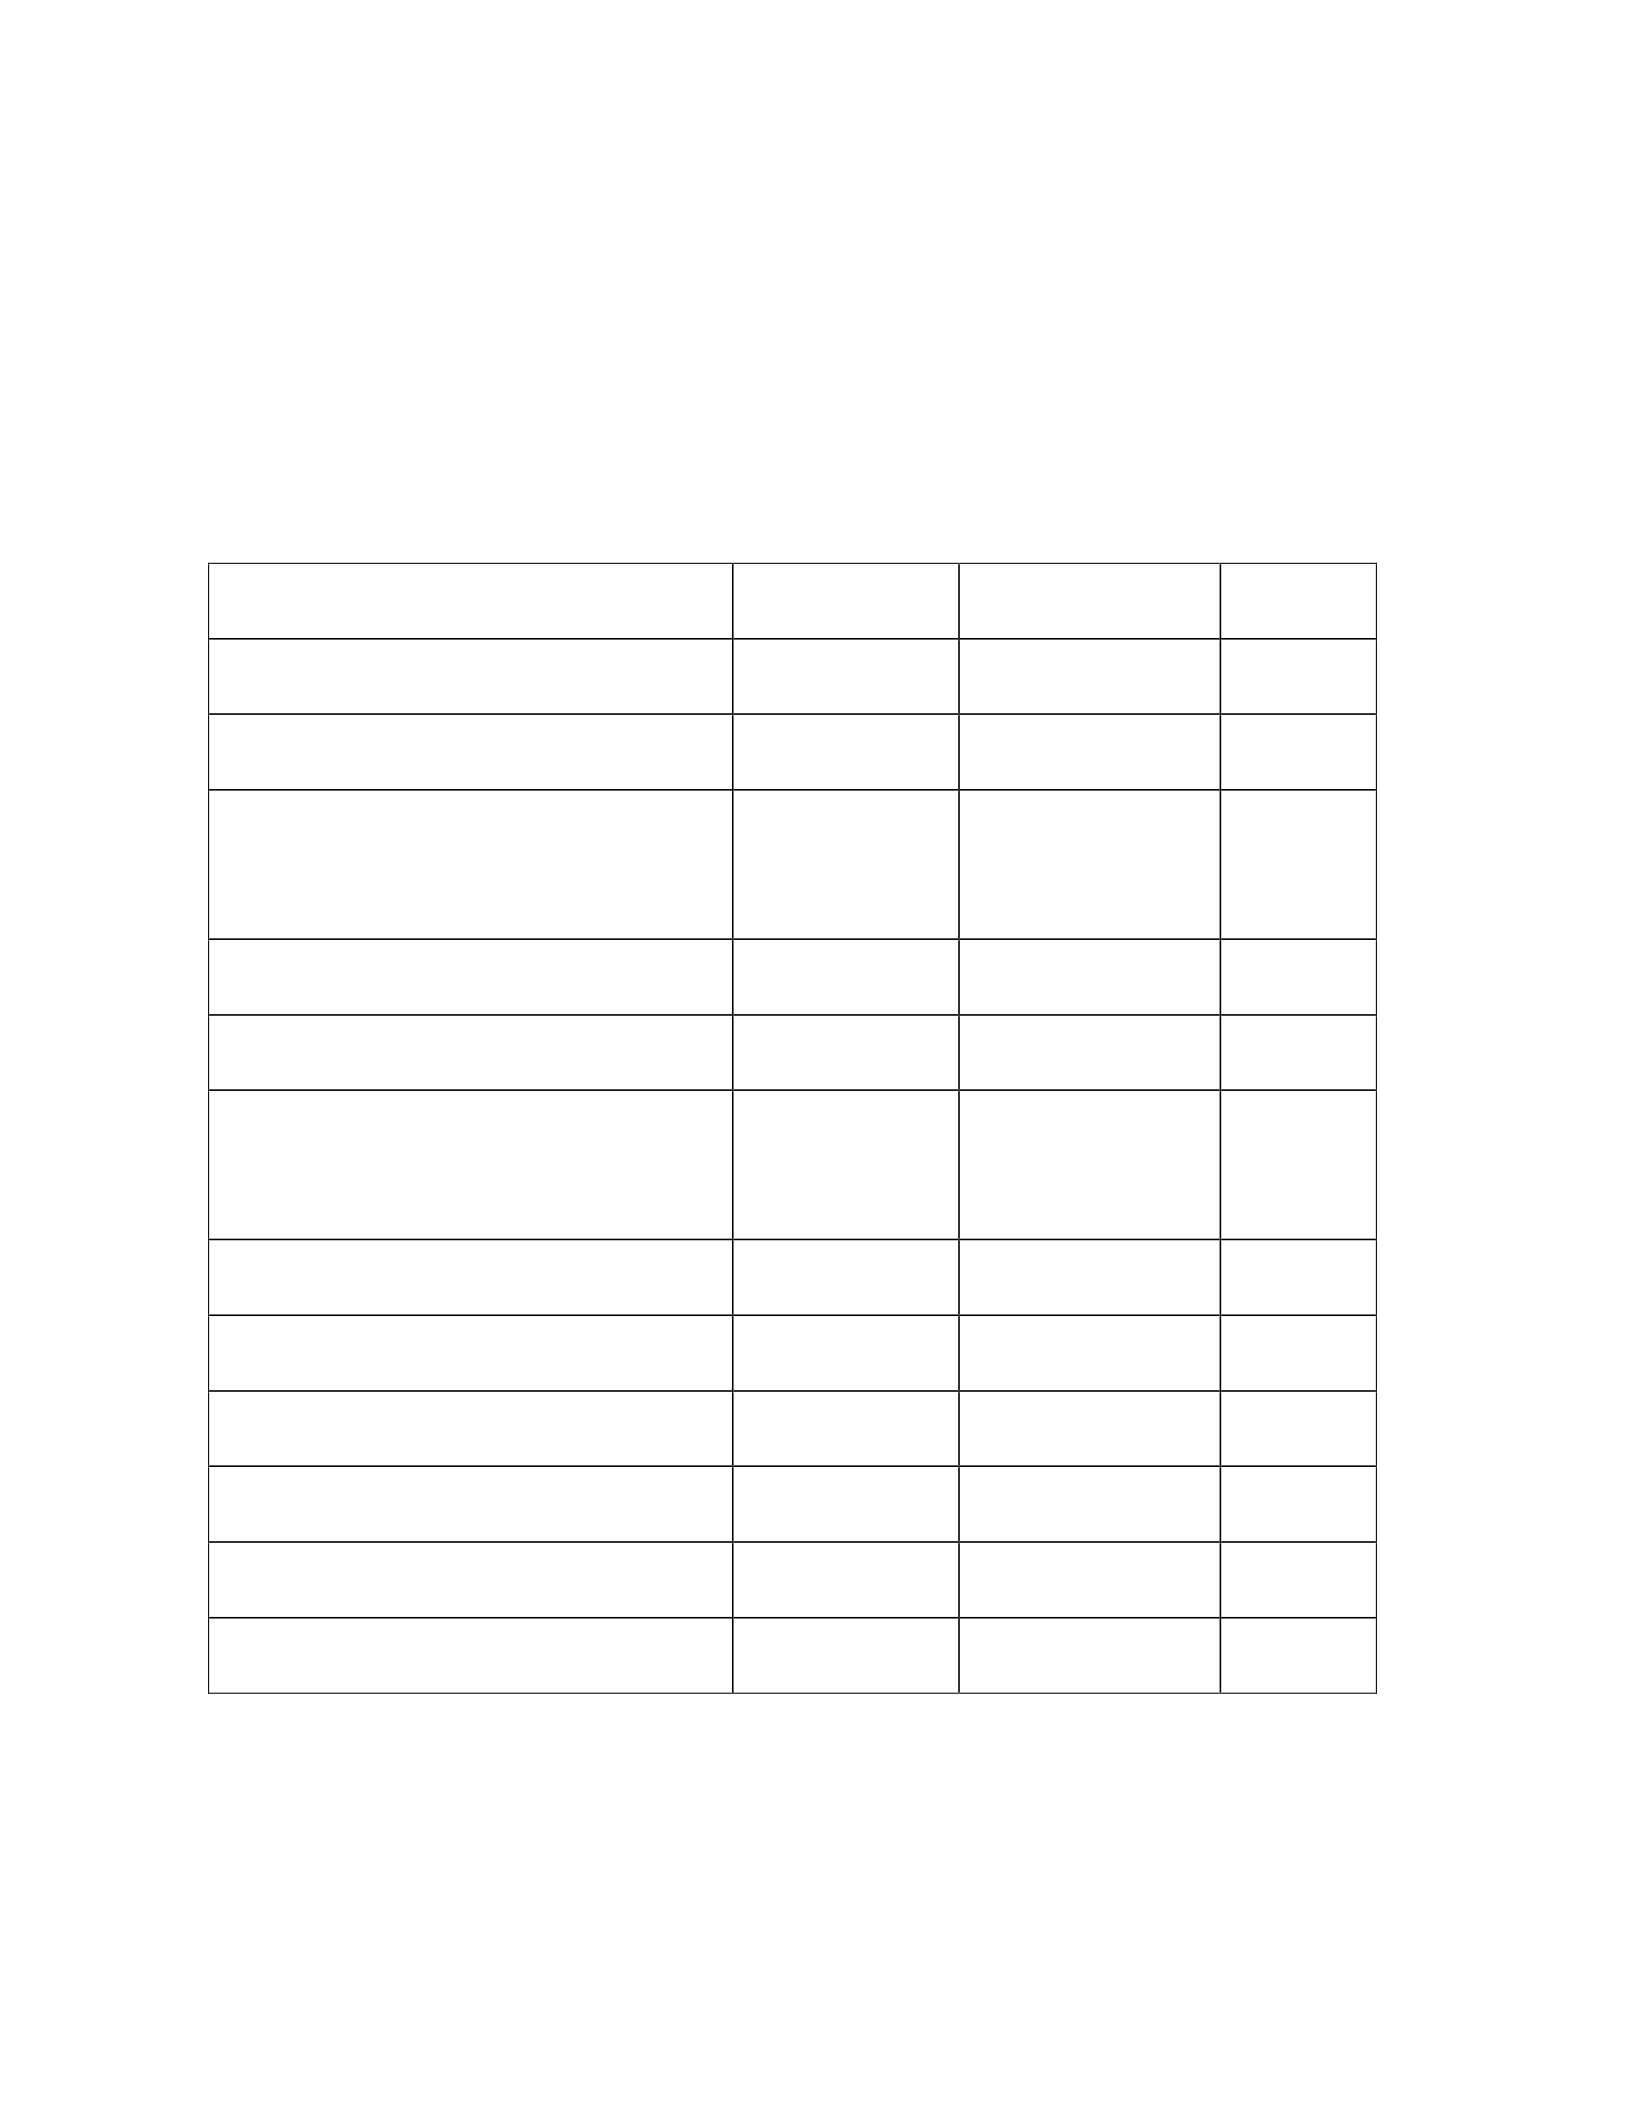
Resistance training successfully reduced the whole-body respiratory exchange ratio
(RER), increased serum free fatty acid (FFA) concentrations and ex vivo muscle palmitate
oxidation, thus confirming that lipid oxidation is preferable to carbohydrate oxidation (Table
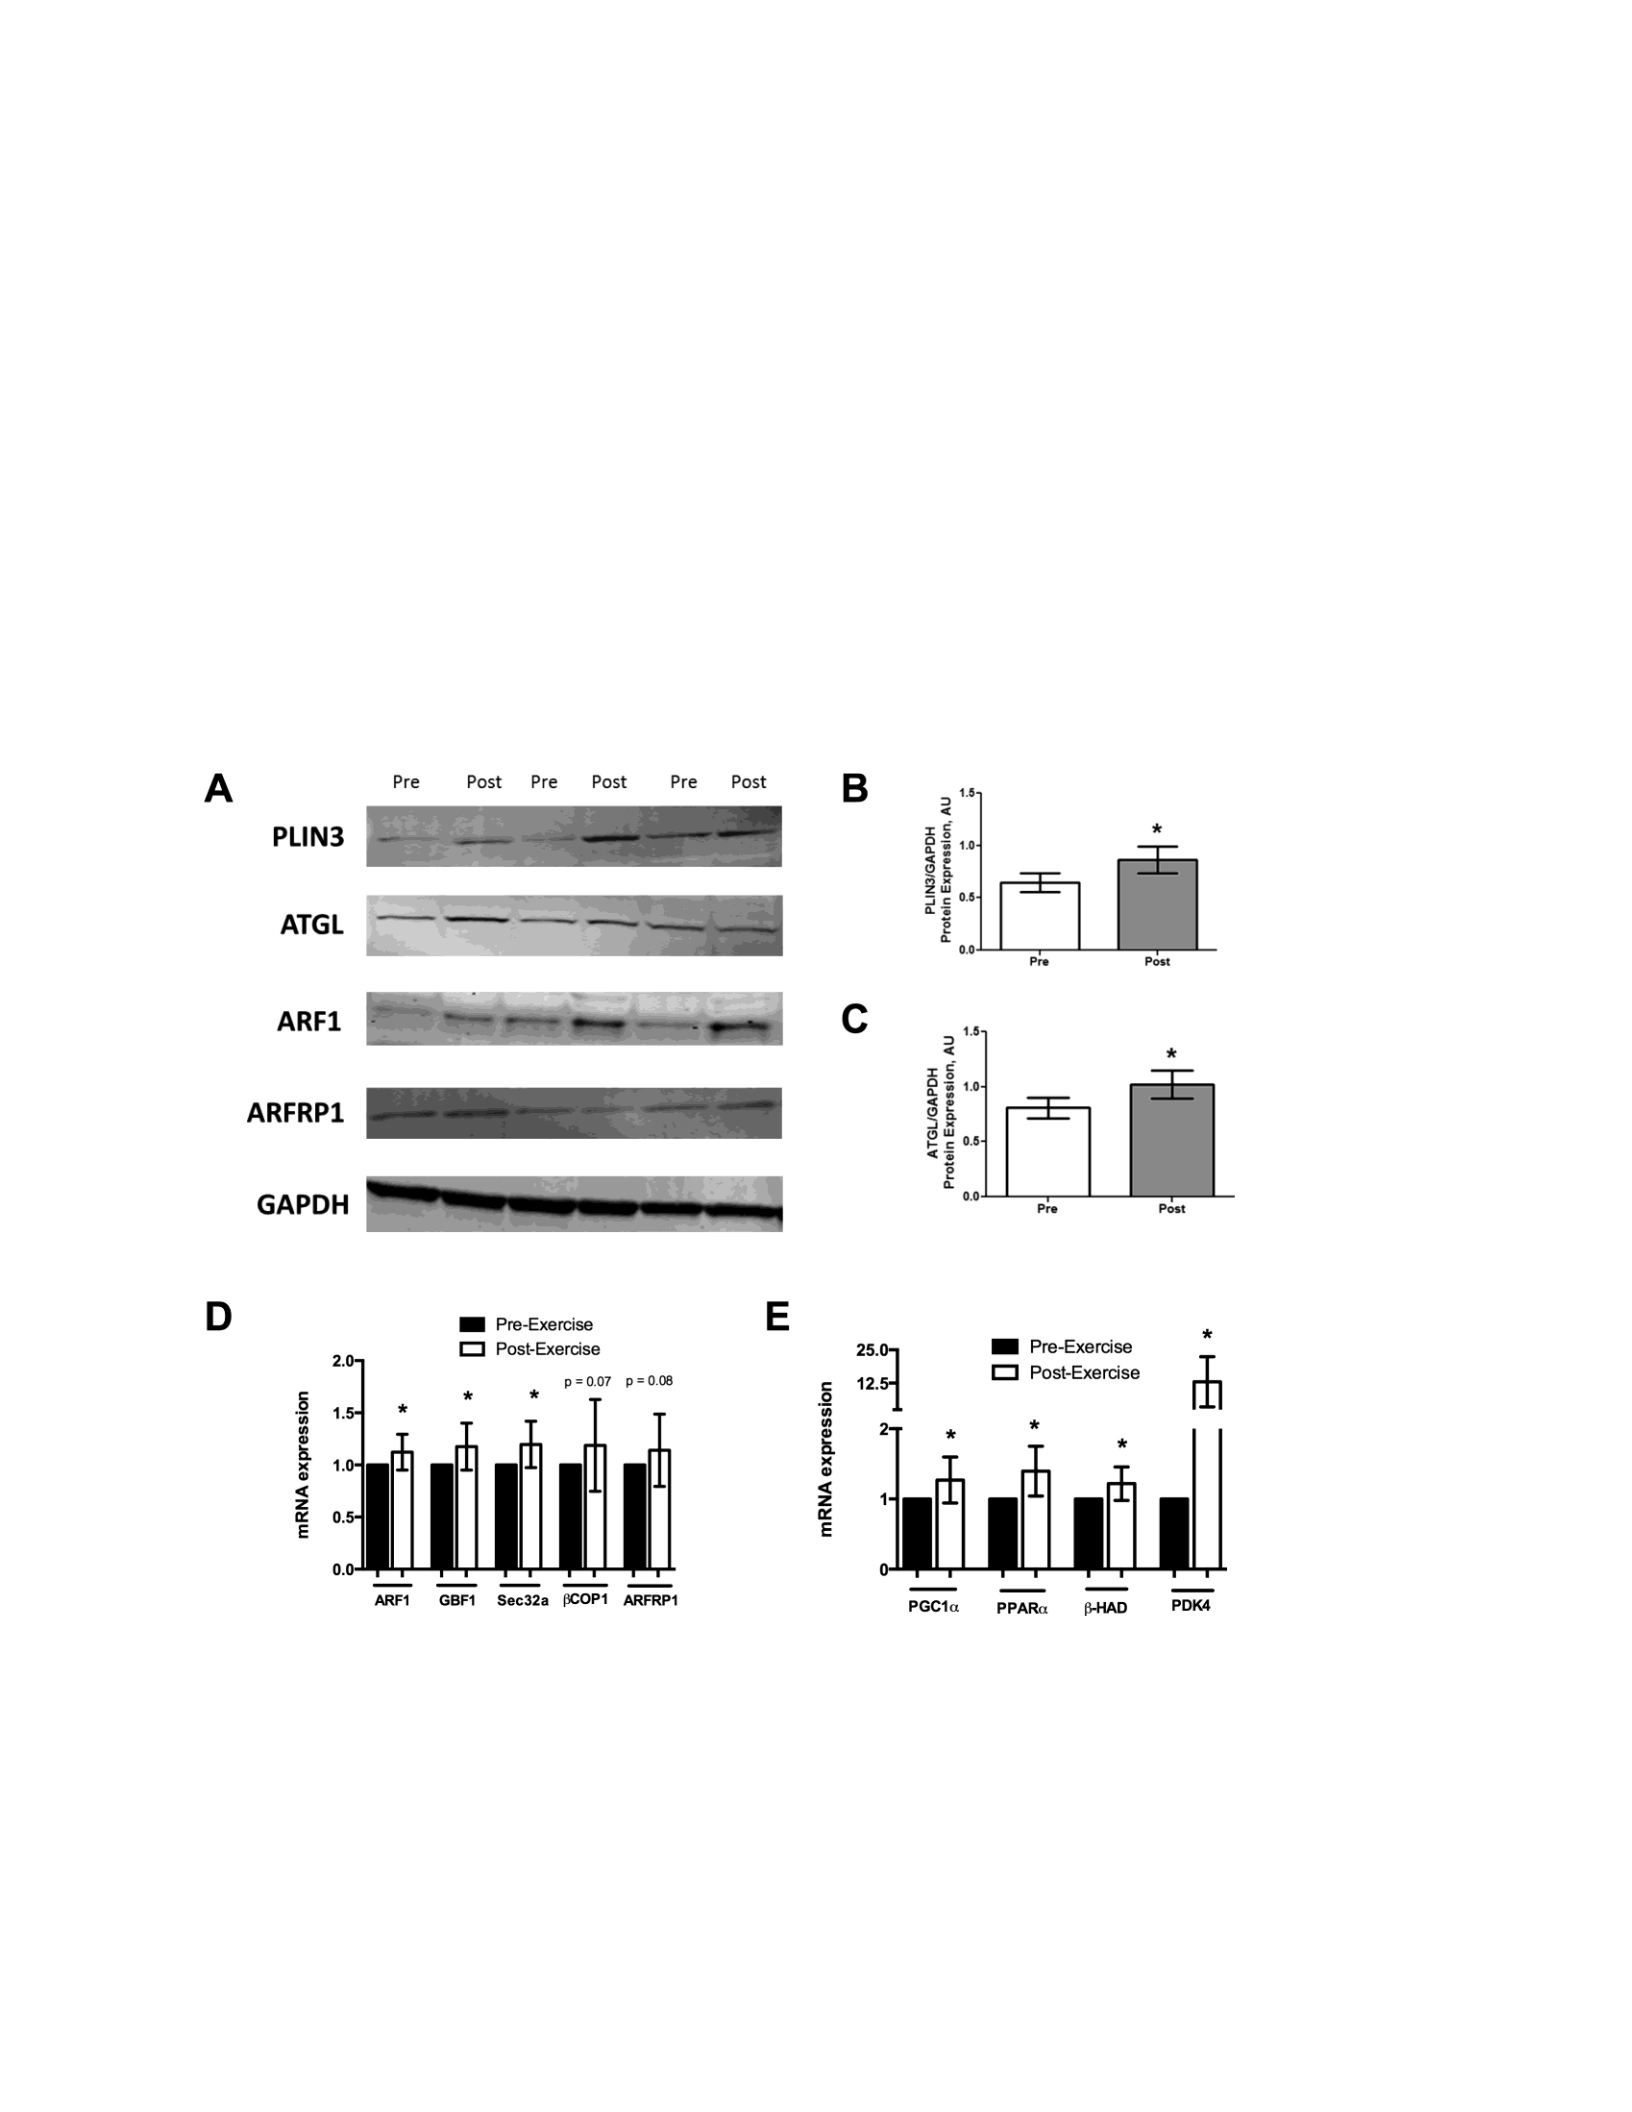
2.2). In line with the increase in lipid oxidation, the protein content of PLIN3 and ATGL
increases with exercise (Figures 2.3A, 2.3B and 2.3C). Similarly, the coatomic GTPase ARF1
increases at the protein and mRNA levels (Figures 2.3A and 2.3D); arfrp1, gbf1, sec23a, and
βcop1 increase only at the mRNA level (Figure 2.3D). Good pparα, transcription
Known factors regulate the expression of the perilipin protein family [66-68], and its coactivator
PGC1α
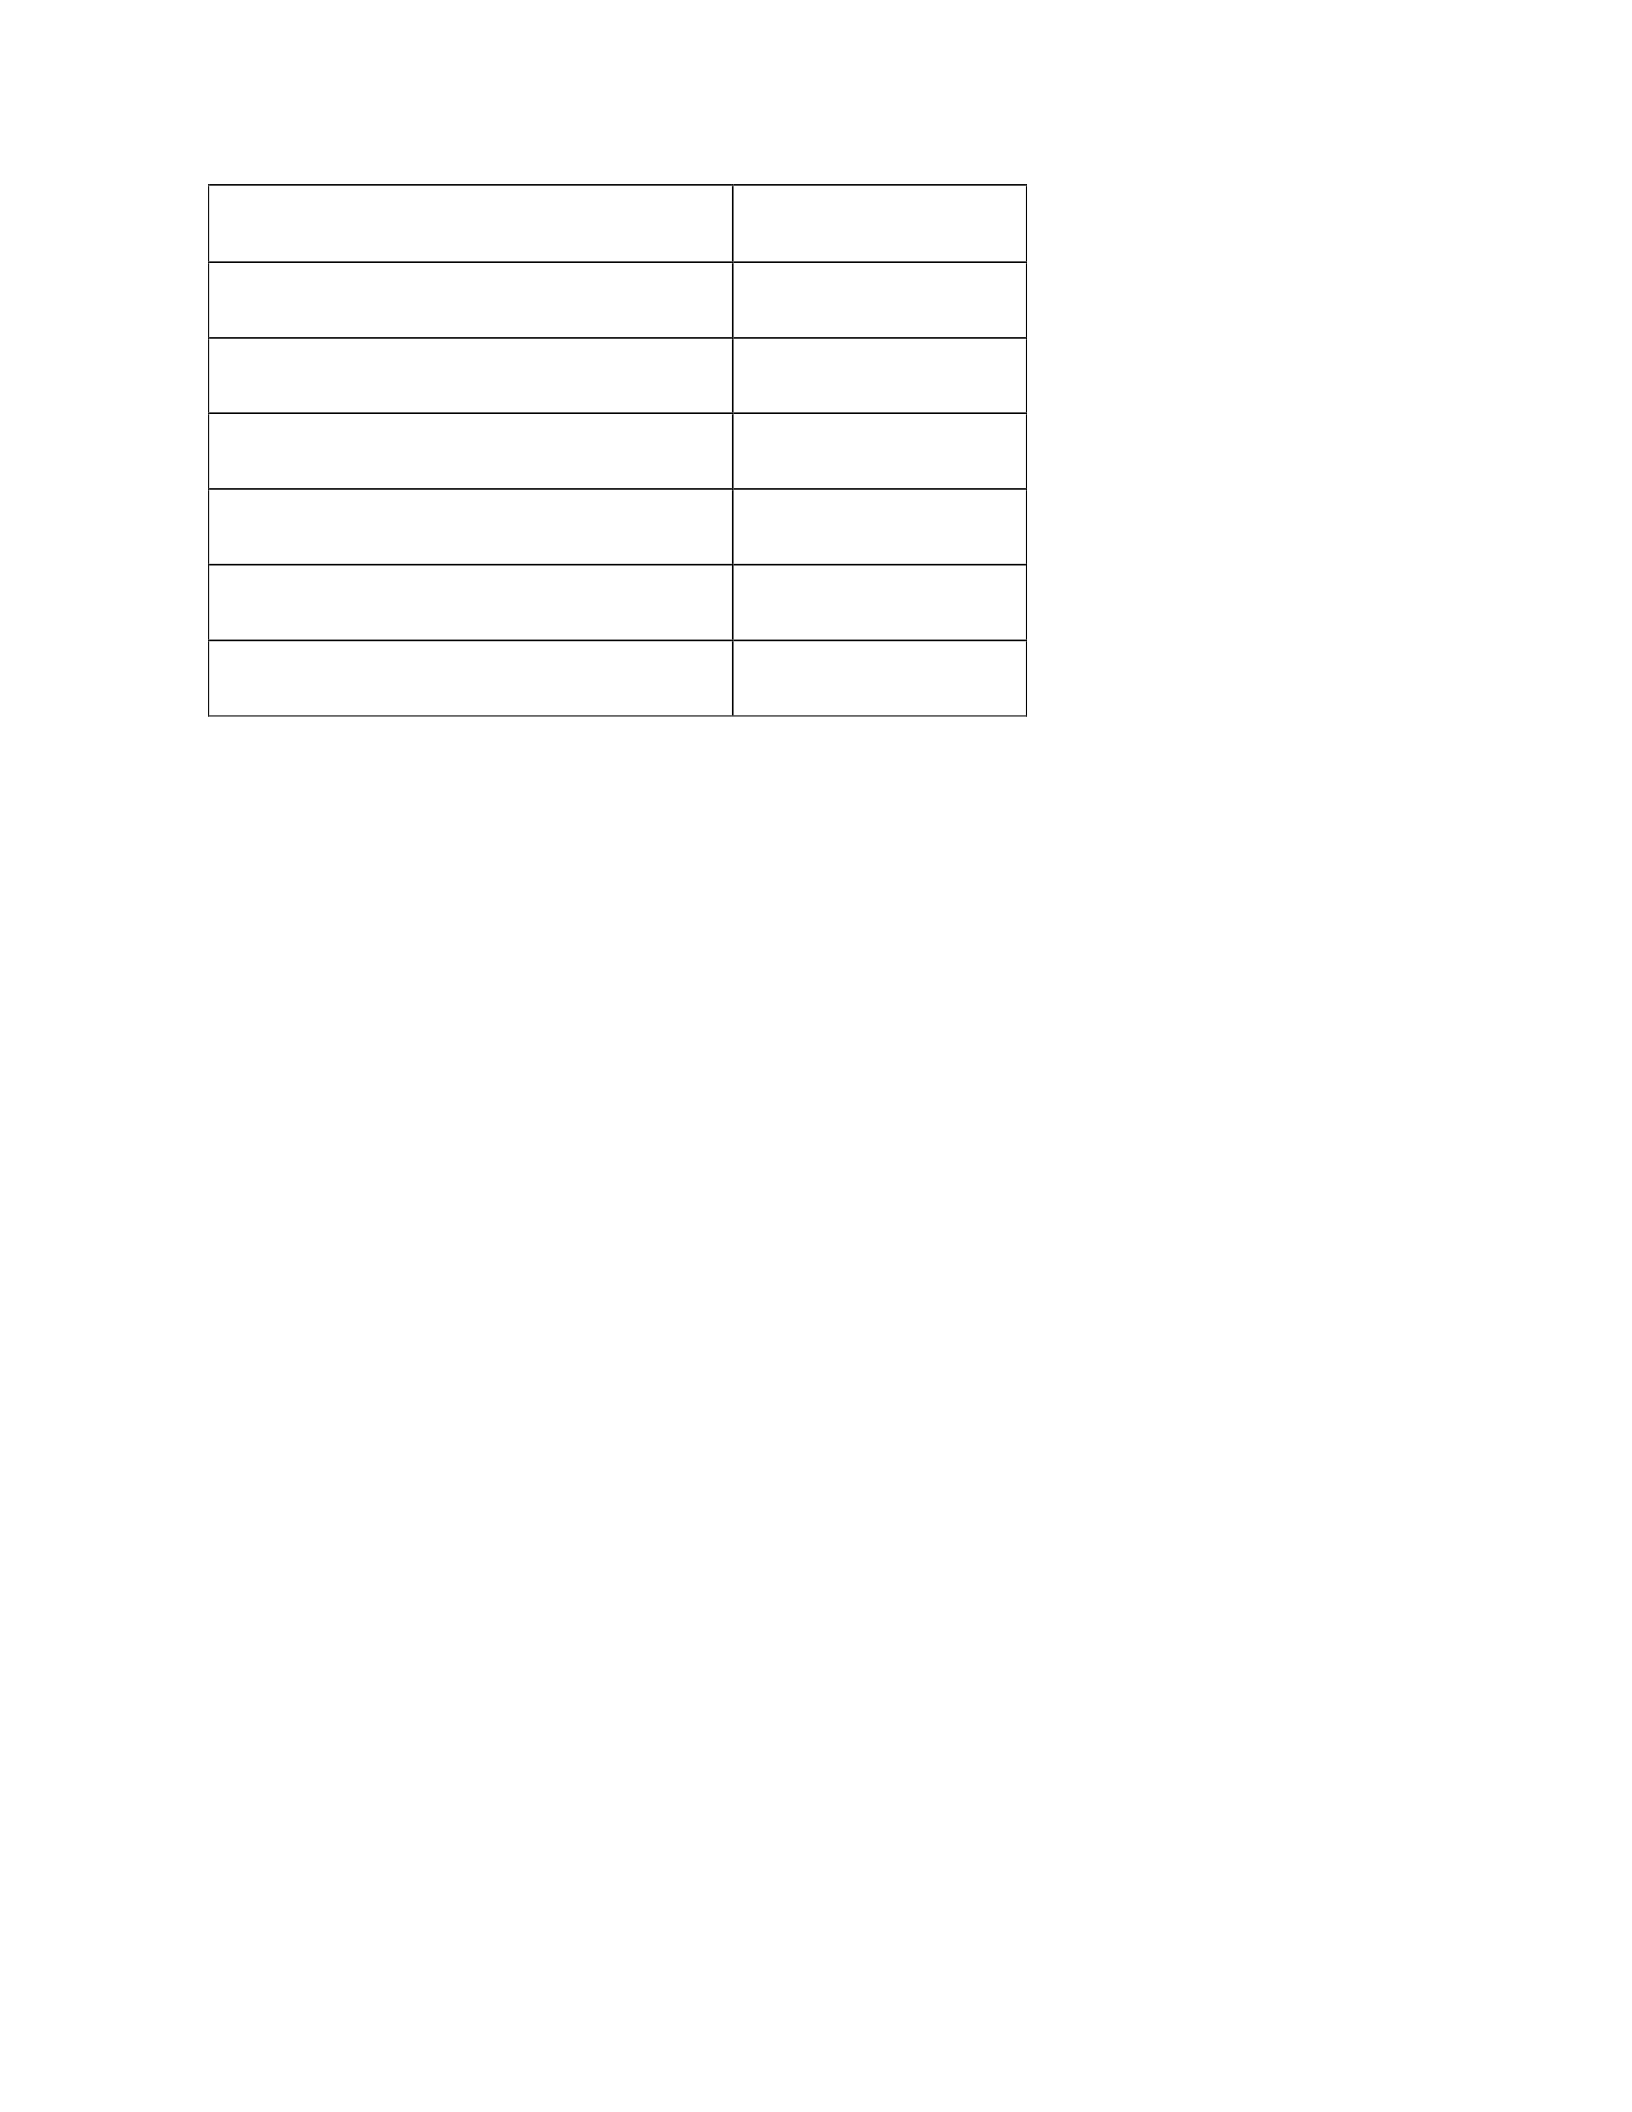
Table 2.1. Anthropometric characteristics of participants in Single Endurance Exercise.
BMI, body mass index; FM, fat mass; FFM, fat-free mass; HOMA-IR, homeostatic model
assessment for insulin resistance; FFA, free fatty acids
Mean ± SD
Age (yrs)
24.0 ± 4.5
Weight (kg)
76.7 ± 6.5
Height (cm)
180.3 ± 5.4
BMI (kg/m2)
23.6 ± 1.8
% Body Fat
16.6 ± 3.2
FM (kg)
12.8 ± 3.1
FFM (kg)
63.9 ± 4.7
26
VO2Max (mL/mnt/FFM)
47.2 ± 5.7
Glukosa Puasa (lime/dL)
88.0 ± 4.6
Insulin Puasa (mU/dL)
3.6 ± 1.6
HOMA-IR
0,78 ± 0,37
FFA Fasting
0,45 ± 0,17
Fiber % Type 1
35.9 ± 11.7
Fiber % Type 2
64.2 ± 11.7
increased their mRNA expression with exercise. The expression of mRNA βhad and pdk4, two
enzymes that support fat oxidation, also increased with exercise, further confirming the
preferred lipid oxidation in skeletal muscle with exercise (Figure 2.3E).
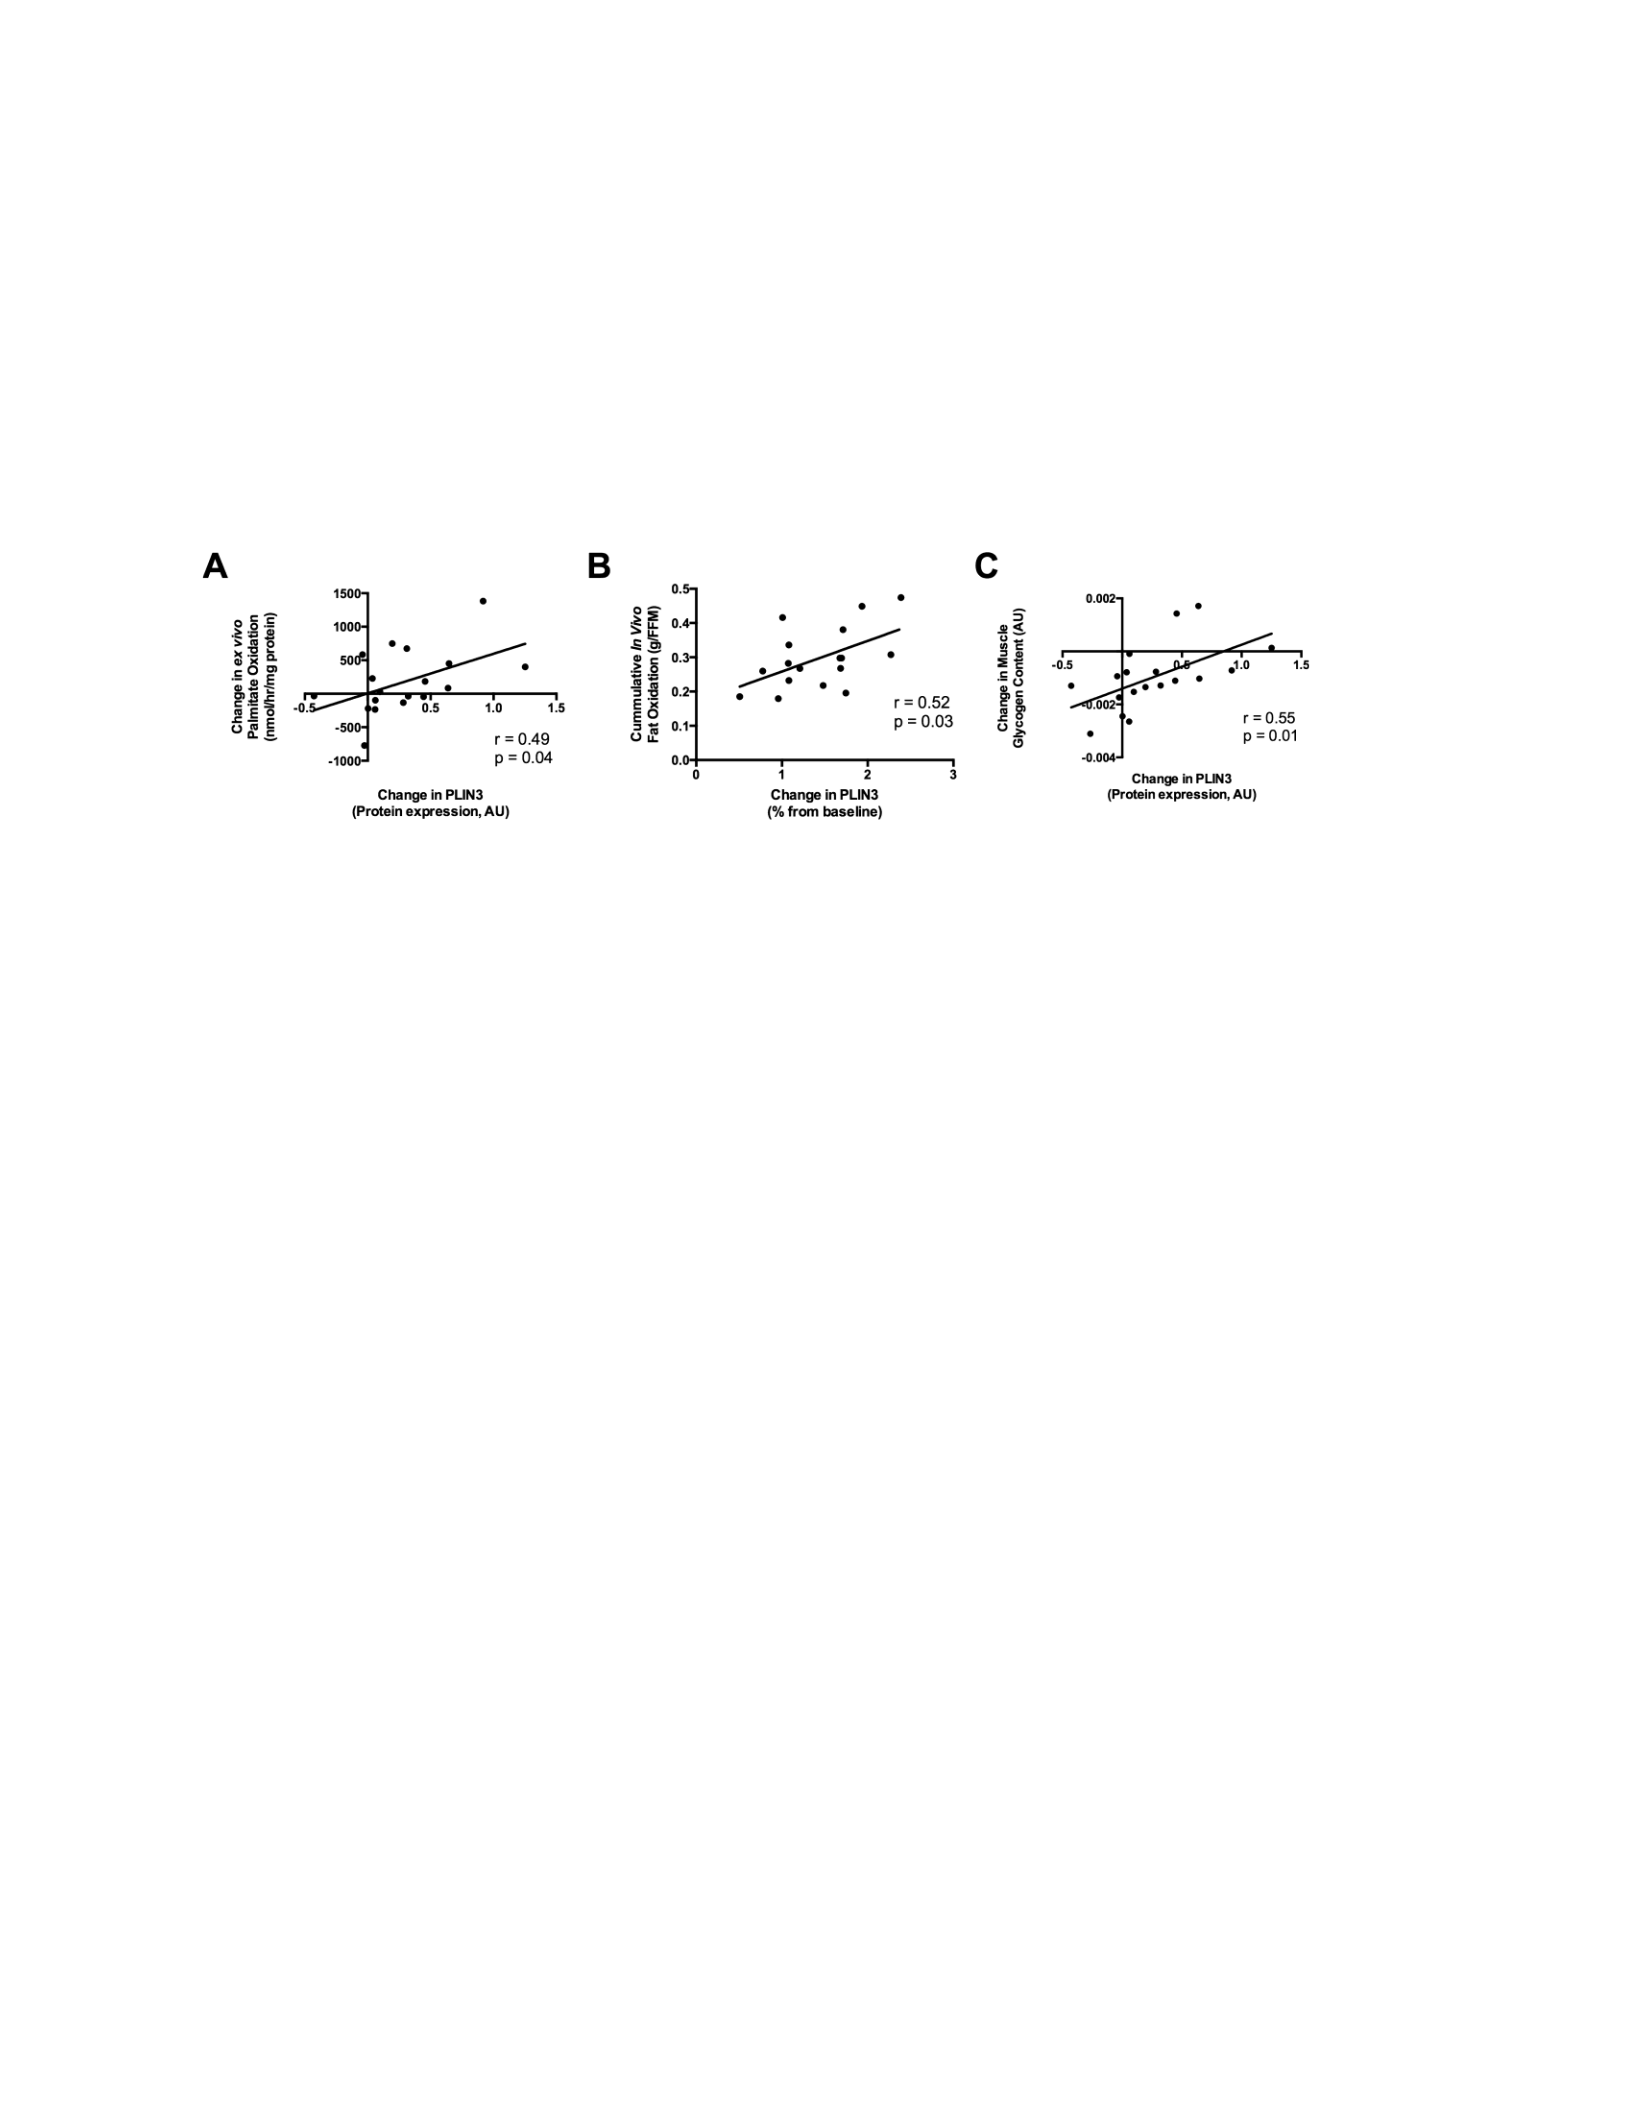
Changes in PLIN3 protein with exercise were positively associated with changes in
palmitate oxidation of ex vivo muscle (r = 0.49, p = 0.04; Figure 2.4A) and with cumulative
whole-body fat oxidation after adjusting for fat-free mass (FFM; r = 0.52, p = 0.03; Figure 2.4B).
We noted a slight decrease in IMCL content; however, despite the increase in vivo and ex vivo
fat oxidation, the decrease in IMCL content did not reach significance (p=0.21, Table 2.2). We
found that people who increased PLIN3 with exercise tended to have the opposite
27
relationship with IMCL change (r = -0.35, p = 0.10). However, after adjusting for the fiber-type
cross-sectional area, a measure referred to as IMCL density, participants who increased PLIN3
Table 2.2. Clinical characteristics and muscle fibers before and after a single resistance
training fight. RER, respiratory exchange ratio; IMCL, intramyocellular lipid content; FFA, free
fatty acids.
Basis
Post Training
Mean ± SD
Mean ± SD
P value
MORE
0,95 ± 0,04
0,89 ± 0,03
<0.001
Oxidation Palmitate, ex vivo
(protein NMOL / jam / mg)
615,9 ± 375,9
887,3 ± 404,3
0.01
Total IMCL Content (AU)
27,7 ± 27,5
21.3 ± 19.4
0.21
IMCL content in type 1 (AU) fibers
29.3 ± 28.6
23.4 ± 22.6
0.21
Content of IMCL in type 2 fibers
(AU)
25.9 ± 25.9
20.1 ± 17.9
0.25
IMCL Fiber type 1 density (AU)
11.2 ± 13.6
7.9 ± 7.5
0.24
IMCL Fiber type 2 density (AU)
16.3 ± 16.9
13.3 ± 13.3
0.40
Glycogen Content (AU)
8.40 ± 0.79
7.32 ± 0.68
0.001
FFA (mmol/L)
0.45 ± 0.17
0.73 ± 0.30
<0.001
Epinefrin (mg/dL)
46.9 ± 17.8
193.4 ± 77.5
<0.001
Norepinefrin (mg/dL)
302.2 ± 149.0
986.2 ± 347.6
<0.001
28
protein content with exercise had a significant inverse correlation with IMCL density in type II
fibers (r = -0.58, p = 0.02); while there was no association with IMCL density in type I fibers (data
not shown). As expected, the glycogen content in skeletal muscles decreased significantly after
exercise (p=0.001, Table 2.2). Changes in PLIN3 protein content were positively related to
changes in glycogen (r = -0.55, p = 0.01; Figure 2.4C), showed that participants who increased
their PLIN3 preferred lipid oxidation to carbohydrate oxidation during exercise.
Changes in the PLIN3 protein, however, have no association with changes in serum FFA, epinephrine
or norepinephrine concentrations.
Figure 2.3. Changes in the expression of proteins and genes related to lipolysis with a single
attack of resistance training in human skeletal muscle. A) PLIN3, ATGL, ARF1, ARFRP1
29
representative blocks and GAPDH loading control. B) Quantitative bar graph of PLIN3 protein
of skeletal muscle after acute exercise (n=19). C) Quantitative bar graph of skeletal muscle ATGL
protein after acute exercise (n=19). D) lipid droplet coatomic gene mRNA levels (n=19), and (E)
oxidative gene mRNA levels, in skeletal muscles of healthy subjects in response to acute exercise
attacks (n=14-19). *P < 0.05.
Figure 2.4. The association between changes in perilipin protein 3 (PLIN3) in skeletal
muscle tissue and fat oxidation. A) Correlation between changes in PLIN3 protein expression
and ex vivo palmitate oxidation changes measured from skeletal muscle tissue homogenates (n
= 18). B) Correlation between percentage change in PLIN3 protein expression and whole-body
cumulative fat oxidation measured by indirect calorimetry adjusted for fat-free mass (n=18). C)
Correlation between changes in total glycogen content and changes in PLIN3 protein during
exercise (n = 18).
2.4 Discussion

30
Perilipin 3 is a lipid droplet layer protein that has previously been shown to co-localize to
lipid droplets and with ATGL on lipolysis stimulation [44, 45]. Our data show for the first time in
human primary muscle cells that PLIN3 expression increases in response to epinephrine
stimulation and pharmacological cocktails that are known to induce lipolysis. Importantly, we also
showed for the first time that PLIN3 expression increased in vivo , in skeletal muscle tissue of
healthy, lean men after long resistance training. The increase in PLIN3 protein was positively
correlated with the oxidation of ex vivo muscle homogenate palmitate as well as the oxidation of
whole-body cumulative fat with exercise.
Our data support the hypothesis that PLIN3 is involved in lipid oxidation in skeletal
muscle. Prats et al. showed that in individual rat muscle fibers, PLIN3 colocalized to lipid droplets
after administration of epinephrine [43]. Smirnova et al. showed that during lipolysis, ATGL co-
localizes to lipid droplets coated with PLIN3 and replaces PLIN3 along the surface lipid droplets
[44]. Our PFI treatment in human myotubes showed that PLIN3 increased immediately after the
cessation of the lipopolitical stimulus (Figure 2.1B). In addition, PLIN3 expression increased from
immediately after PFI treatment to 30 min, while maximum expression of ATGL immediately
after PFI treatment with a steady decrease in its expression after lipolysis stimulation (Figure
2.1B). This supports the concept referred to in Smirnova et al. which states that ATGL replaces
PLIN3 during lipolysis. Furthermore, we showed that PLIN3 in myotubes increased in response
to in vitro as well as in vivo epinephrine stimulation after resistance training (Figures 2.1A, 2.3A,
and 2.3B). The increase in PLIN3 protein content in tissues was positively associated with changes
in the oxidation of ex vivo palmitate in skeletal muscle (Figure 2.4A), cumulative whole-body fat
oxidation (Figure 2.4B), and with changes in glycogen content in muscles (Figure 2.4C). People
who increased their PLIN3 protein content with exercise, had a tendency towards an inverse

31
relationship with changes in IMCL content with exercise (data not shown). Together, these data
suggest that the PLIN3 protein is involved in lipolysis induced by in vitro pharmacological
stimulation or by resistance training in skeletal muscle.
Our data also showed an increase in some coatomic GTPases after lipolysis stimulation
both in vitro and in vivo. Previous experiments have shown that knockdown βCOP1, ARF1,
GBF1, or Sec23a prevents the colocalization of ATGL to PLIN3-coated lipid droplets [47]. Guo
et al. hypothesized that coatomic GTPase is involved in lipid droplet partitioning for lipolysis and
lipase interactions [22]. However, no direct protein-protein interactions between ATGL and
PLIN3 have been observed [32]. Therefore, we speculate that the increase in PLIN3 along with
the coatomer GTPase suggests that PLIN3 facilitates lipolysis by serving as a targeting signals to
direct the delivery of lipase to lipid droplets. Our data reported here, although new, are
observational and the actual mechanism of this relationship cannot be fully explained from this
study. Future proteomic investigations will be needed to conclusively extrapolate the definitive
mechanisms for their interactions.
One limitation of our study was that although we recruited 20 male participants, we were
only able to conduct molecular investigations on 14 to 19 participants for some of our actions, due
to the limited amount of skeletal muscle tissue. In addition, since we collected biopsy samples at
the beginning and immediately after exercise exercise, we were only able to exert an acute effect
of exercise on the PLIN3 content. The inverse correlation between the change in PLIN3 and the
density of IMCL in type II fibers was observed but could not be explained based on our current
data. Future studies of fiber type-specific IMCL and PLIN3 expression may provide insight into
these correlations. In addition, based on this observational study, we were unable to provide insight
into why the maximum expression of mRNA and the level of the GTPase protein investigated
occurred at different time points after lipolimic stimulation (Figures 1A and 1B). We can only

32
state that the increase in GBF1, ARFRP1, ARF1, Sec23a, and βCOP1 occurs at either the mRNA
level, the protein level or both at some time point after lipolimic stimulation. However, it is
important to note that this is the first study to show an increase in PLIN3 and coatomic GTPase in
human skeletal muscle after lipolysis stimulation using both in vitro and in vivo
experiments.Future studies will be needed to determine the effects of lipopolitical stimulus
duration, signal transduction, co-localization, and protein-protein interactions between PLIN3 and
coatomic GTPase in skeletal muscle lipid metabolism. Interestingly, Louche et al. recently
reported an increase in regulation of PLIN3 protein content after 8 weeks Endurance Training
Exercises [69]. Future studies should also be conducted to determine the chronic effects of exercise
and different types of exercise on PLIN3 in relation to lipid oxidation.
In conclusion, our data show for the first time that increased expression of perilipin 3 and
coatomer-related targets involved in the transport of ER-to-Golgi cargo with exercise is associated
with exercise-stimulated lipolysis in skeletal muscle. These data offer a potential pathway that has
not been previously explored for the regulation of lipase access to nascent lipid droplets or
fragmentation and regulation of lipolysis in skeletal muscle. This may provide further insight into
potential irregularities in skeletal muscle fat oxidation, which has been shown to occur in obesity,
type 2 diabetes and lipodystrophy.

33
CHAPTER 3: PERILIPIN 3 DIFFERENTLY REGULATES SKELETAL MUSCLE LIPID
OXIDATION IN ACTIVE, SEDENTARY, AND TYPE 22 DIABETIC MEN
3.1 Introduction
Lipid oxidation disorders along with increased intramyocellular lipid (IMCL) levels are
the main characteristics of skeletal muscle pathophysiology associated with T2D . It has been
shown that decreased insulin sensitivity in skeletal muscle is strongly associated with increased
IMCL content [13]. However, Goodpaster et al. showed in 2001 that athletes, who are highly
sensitive to insulin also have high levels of IMCL known as the athlete's paradox [15]. Efforts
to understand lipid storage and utilization in skeletal muscle are important to provide insight
into the athlete's paradox.
The storage and packaging of lipid droplets in skeletal muscle has recently become an
important area of research. Many studies have focused extensively on perilipin 5 (PLIN5), which
is expressed in skeletal muscle, [28] and has been shown to be associated with lipid metabolism
[28, 31-33, 35, 53, 56, 70]. Unfortunately, another lipid droplet protein that is highly expressed in
skeletal muscle [28], perilipin 3 (PLIN3), has been neglected. Studies conducted on rat skeletal
muscle have shown PLIN3 colocalized to lipid droplets during catecholamine stimulation and also
after muscle contraction [43]. Other studies have shown that ATGL colocalizes to PLIN3-coated
lipid droplets during lipolysis stimulation [44, 45]. Although ATGL does not interact directly with
PLIN3 [32], other investigations have shown that coatomic GTPases, such as ADR-ribosylation
factor 1 (ARF1), ARF-related peptide 1 (ARFRP1), and Golgi-
Brefeldin A resistance factor 1 (GBF1), is involved in the pathway that delivers ATGL to PLIN3-

34
coated lipid droplets, thereby facilitating lipid oxidation [47, 71]. We recently demonstrated the
possible role of PLIN3 on skeletal muscle lipid oxidation using in vitro and ex vivo exercise
models [72]. However, despite these observational studies, the role of PLIN3 for skeletal muscle
lipid oxidation has not been widely investigated. To our knowledge, no studies have examined
the lipid oxidation of skeletal muscle after knockdown of PLIN3 in skeletal muscle cells, nor has
the differential expression of PLIN3 and PLIN5 been investigated in the myotubes of the active
substance, T2D, or metabolically healthy lean subjects after lipolysis stimulation.
Therefore, we aim to conduct an investigation in three phases to examine the effects of
PLIN3 on skeletal muscle lipid oxidation. First, we conducted a clinical investigation on 29
sedentary, healthy, non-obese, normochromic men to examine the association between the
expression of skeletal muscle protein PLIN3 and whole-body fat oxidation measured using a 24-
hour metabolic chamber and ex vivo skeletal muscle-specific lipid oxidation. Second, we bred
primary myotubes from these five participants to determine the role of PLIN3 on lipid oxidation
by knocking down PLIN3. Finally, we compared the protein content of PLIN3 and PLIN5 after in
vitro pharmacological lipopolitical stimulation (Palmitate, Forskolin, and Ionomycin, PFI
cocktails), as well as lipid oxidation after treatment with brefeldin A (BFA), pharmacological
compounds shown to inhibit ARF1 and PLIN3-related coatomer [47] in primary skeletal muscle
myotube cultures from active, sedentary, and T2D donors. We hypothesize that PLIN3 will be
associated with the oxidation of specific lipids throughout the body and muscles, and that
knockdown of PLIN3 in the primary human myotube will result in lower lipids

35
Oxidation. We also hypothesize there will actually be differential expression of PLIN3 and
PLIN5 in primary skeletal muscle cultures from these three cohorts, and that it would be a
differential lipid oxidation response to BFA treatment from these cohorts.
3.2 Method and Materials
3.2.1 Clinical Studies and Skeletal Muscle Biopsy Procedures
Twenty-nine sedentary, normogchemic male participants were recruited into the EAT trial
(Clinicaltrials.gov#: NCT01672632) and underwent body composition measurements (dual-
energy x-ray absorptiometry [DXA], QDR 4500A; Hologics, Waltham, MA; and MRI, 3.0T
magnet, Excite HD System; General Electric, Fairfield, CT), fasting blood serum measurement,
euglycemic hyperinsulinemic clamps to measure insulin sensitivity, and 24-hour breathing
chamber to measure 24 energy metabolism. All anthropometric and metabolic characteristics are
provided in Table 1. Vastus lateralis muscle biopsies were obtained to measure protein content (n
= 26), ex vivo palmitate oxidation (n = 15), and to establish primary myotube cultures in five lean
and healthy (skinny) male donors. As a secondary study, skeletal muscle biopsies were obtained
from vastus lateralis from four physically active (active) thin male donors, and four obese type 2
(T2D) diabetic male donors to build primary skeletal muscle cultures for cross-sectional
comparison with sedentary and lean donors. The anthropometric and metabolic characteristics of
the active, T2D, and subset of the five lean participants, in which primary muscle cultures were
examined, are provided in Table 2. Active subjects were recruited based on their physical activity
level habitual level, if they were between 20-40 years old, BMI 20-30 kg/m2, non-diabetic, not
taking medication, and otherwise healthy.

36
Physical activity level is calculated from the withdrawal of the 7-day physical activity questionnaire
and The triaxial accelerometer is used for at least 4 days. The physical activity index (total daily energy
expenditure/resting metabolic rate) was calculated using both methods and the daily activity level was
researched from the accelerometer data to ensure that the active subjects had an activity index greater
than 1.6. Another inclusion criterion for active participants was VO2max above 40 ml/kg/min. Active
participants are enrolled in the ACTIV trial (Clinicaltrials.gov #: NCT00401791). T2D participants
are enrolled in the TAKE TIME trial (Clinicaltrials.gov#: NCT00401791), if they have known type 2
diabetes mellitus, are weight stable, healthy, and are allowed to take metformin, insulin and/or
sulfonylureas, but not thiazolididediones. All participants gave written consent, and all trials were
reviewed and approved by the Pennington Biomedical Research Center's Institutional Review Board.
The anthropometric and clinical metabolic characteristics of the study participants were carried
out as follows: 24-hour whole-body metabolism was measured using the metabolic chamber as
described earlier [73]; in vivo assessment of basal and maximum mitochondrial ATP production
of skeletal muscle was carried out under magnetic resonance spectroscopy (3T Signa Excite MRI;
General Electric, Milwaukee, WI) as described earlier [74, 75]; Eugligamy-hyperinsulinemic
clamps were performed for ACTIV and TAKE TIME trials as previously described using a 120-
minute protocol and an 80mU/min/m2 insulin infusion [75] and for the EAT trial as described
earlier using a 120-minute protocol and a 50mU/min/m2 insulin infusion [76]; fasting serum sizes
were assessed in a certified clinical chemistry laboratory. We reported cross-sectional measures
of clinical data for GDR, 24-hour energy expenditure, and mitochondrial ATP production (a
surrogate marker for VO2ma [75]) to show that there was indeed a difference between insulin
sensitivity and physical fitness of active participants

37
Skeletal muscle samples were collected after overnight fasting using the Bergstrom technique
with suction (Propper Manufacturing Co., Long Island City, NY) from vastus lateralis after
administration of local anesthesia lidocaine/bupivicaine. Clinical procedures were performed in
the same order for all participants with MRI/MRS procedures performed first followed by a
stent in the metabolic chamber for 24 hours. The participants then performed a skeletal muscle
biopsy in the morning when they exited the metabolic chamber, and then underwent a clamping
procedure.
3.2.2 Mitochondrial Capacity Assessment in vivo
Mitochondrial capacity is assessed both as the maximum rate of ATP production
(ATPmax) and the demand/rate of basal ATP ATPase (ATPase). Both are measured ATPmax:
Maximum mitochondrial capacity is assessed in the lateralis vastus by measuring the time constant
(tau) required for Phosphocreatin (PCr) recovery after 45 seconds of quadriceps isometric
contraction and PCr levels in resting oxygenated muscle (resting PCr): ATPmax = PCrrest/tau.
Participants were asked to lie on their backs at the patient's desk 3.0 Tesla Magnetic Resonance
Imager/Spectrometer (GE Excite) for approximately 45 minutes. After a reconnaissance scan to
locate the lateral vastus a baseline concentration of PCr, ATP, and Phosphate (Pi) ions; during the
participants were then asked to perform isometric contractions of the quadriceps muscles for 45
seconds with a frequency of 1 contraction/second to deplete the PCr reserve.

38
PCr store refills are assessed after 45 seconds of isometric exercise. ATPase: The rate of ATPase
is measured by the rate of breakdown of PCr in anosic muscles, which represents the cell's basal
ATP demand. Anoxia in vastus lateralis is induced by inflating the blood pressure cuff around the
upper thigh to 50-60 mm Hg above the systolic blood pressure, thus transporting blood flow and
O2 delievery, and therefore requiring muscles to deplete Mb-O2 and Hb-O2 stores to meet aerobic
respiration needs. Cuff pressure is controlled with the Hokanson Rapid Inflator/Deflator system.
Anoxia/ischemia was induced in the participant's legs for 15 minutes with levels of PCr, ATP, and
Pi assessed in cellular PCr and pH with MRS 1H.
3.2.3 Measurement of Abdominal Subcutaneous and Visceral Adipose Tissue Volume Abdominal
subcutaneous adipose tissue (SAT) and visceral adipose tissue volume (VAT)
rated with a 3.0 T scanner (Excite HD System; General Electric, Milwaukee, WI). Between 240-
340 images were obtained from the highest point of the liver to the genital symphysis and analyzed
by one trained technician using Analyze software (AnalyzeDirect, Overland Park, KS). The
average coefficient of variation for the same three scan readings is 9.9% for VAT and 1.8% for
SAT. The MRI volume was converted to mass using an assumed density of 0.92 kg/L.
3.2.4 Formation of Primary Human Skeletal Muscle Culture and in vitro Treatment with PFI,
Brefeldin A, and Knockdown PLIN3
The formation of human primary muscle cultures has been modified from the protocol as
described earlier [61, 72], and different collected cell lines for the Lean, Active and T2D groups

39
set for the experiment using the protocol described earlier [62]. Myotubes were treated with 30
μM palmitate, 4 μM forskoline, and 0.5 μM ionomycin (PFI cocktail) using an adapted technique
as described earlier [60, 72]. Treatment of Brefeldin A (BFA) is performed in myotubes using a
technique adapted from Soni et al [47]. Briefly, the myotube was maintained in a differentiation
medium for 7 days and then treated for 30 minutes with Brefeldin A (BFA) at a concentration of
1μg/mL (purchased from Sigma, St. Louis, MO). Knockdown PLIN3 is achieved through
silencing of siRNAs using pre-designed siRNAs (Cat no. s19952) in accordance with the
manufacturer's instructions (Life Technologies, Grand Island, NY).
Myotube was differentiated for 7 days and treated with lipofectamine in serum-free media
followed by siRNA incubation with siPLIN3 or siScramble (siSCR, Life Technologies, Grand
Island, NY), or simply exposed to serum-free media for control. The culture is maintained under
serum starvation for 24 hours according to the manufacturer's specifications.
3.2.5 Skeletal Muscle Tissue Size ex vivo and Primary Myotube In vitro Size
Lipid Oxidation
Lipid oxidation is carried out on skeletal muscle tissue as described earlier [63].
Complete lipid oxidation in primary myotubes is measured as 14CO2 release using 100μM [1-14C]
oleic as described earlier with slight modification [78, 79]. The cells were treated with 500μL of radioactive media,
consisting of DMEM low glucose supplemented with 12.5mM HEPES, 1mM L-carnitine and
100μM [1-14C] oleate (1μCi/mL), and maintained in an incubator (37°C, 5% CO2) for 2 hours. At the end of the reaction
period, the plate is placed on ice to stop the reaction, and 400μL of reaction medium is transferred
to a plastic tube, which is sealed with a rubber cap, with the addition of 100μL of 70% perchloric
acid to release 14CO2,

40
trapped in 200 μL of 1 N NaOH. NaOH trapped 14CO2 is detected through scother counting. The data
were normalized to the protein content of each well.
3.2.6 Gene and Protein Expression Measures
Gene expression was performed as described earlier [72] with Real-Time qPCR on the
7900HT Rapid Real-Time PCR system (Life Technologies, Foster City, CA) using TaqMan Gene
Expression Assays-on-Demand (Life Technologies, Foster City, CA). The catalog numbers for
each Assay-on-Demand product are provided as follows: ARF1 (Hs00796826_s1), Sec23a
(Hs00197232_m1), CGI-58 (Hs01104373_m1), PLIN2 (Hs00765634_m1), and RPLPO
(Hs99999902_m1). The expression level is determined against the standard curve and adjusted to
the RPLPO expression. Total proteins for all trials (both in skeletal muscle tissue and in the human
primary myotubule) were collected using RIPA buffer (Sigma, St. Louis, MO) supplemented with
2% Protease Inhibitor Cocktail (Sigma, St. Louis, MO), 2% Phosphatase Inhibitor Cocktail 2
(Sigma, St. Louis, MO), and 2% Phosphatase Inhibitor Cocktail 3 (Sigma, St. Louis, MO). Protein
content was assessed from total protein extracts using western immunoblotting adjusted to
GAPDH (Cat no. AB9484; AbCam, Cambridge, MA). Imaging of western stains is facilitated on
the Odyssey infrared imaging system (LiCor, Lincoln, Nebraska). Antibodies to PLIN3 (Cat no.
NB110-40764) and PLIN5 (Cat no. NB110-60511) were obtained from Novus Biologicals
(Littleton, CO); Antibodies for ATGL (Cat no. AB109251) and ARFRP1 (Cat no. AB08199) were
obtained from AbCam (Cambridge, MA).
3.2.7 Statistical Analysis
Data was analyzed using PRISM GraphPad Software, version 6.0 (GraphPad Software, La
Jolla, CA). Pearson r correlation is used to assess the relationship between PLIN3

41
protein content and lipid oxidation metabolism measures. A one-way ANOVA with Tukey's post-
hoc test was performed to compare the difference between clinical size and myotube in active,
sedentary, and T2D individuals (Table 2 and Figure 4D). A two-way paired student t-test was used
to assess the difference between control and treatment actions on the myotube (Figures 4A, 4B,
and 4C). The myotube experiment was carried out in triplicate. All graphical data are presented
as SEM ± averages, and a p-value < 0.05 is considered statistically significant.
3.3 Result
3.3.1 The PLIN3 protein is associated with whole-body lipid oxidation and ex vivo and
knockdown PLIN3 results in a noticeable decrease in complete lipid oxidation
Twenty-nine male participants (age: 26.8 ± 5.4 years, weight: 81.9 ± 10.3 kg, BMI: 25.5
± 2.3 kg/m2) is considered to be the average insulin sensitive (glucose elimination rate (GDR) 11.51
± 2.54 mg/min/EMBS and fasting glucose levels of 91.0 ± 6.7 mg/dL) and non-obese with a body
fat percentage of 19.4 ± 4.9. Fasting serum lipids showed total triglyceride levels of 87 ± 42
mg/dL, free fatty acids 0.26 ± 0.08 nmol/L, total cholesterol 171 ± 25 mg/dL, HDL-C 55 ± 12
mg/dL, LDL-C 99 ± 23 mg/dL, and total cholesterol to HDL ratio 3.27 ± 0.96 and HDL-to-LDL
ratio 0.59 ± 0.20. These results have been provided in Table 3.1. The protein content of PLIN3
skeletal muscle was inversely proportional to the 24-hour respiratory intelligence (RQ) measured
in the metabolic chamber (Figure 3.1A) and positively correlated with ex vivo palmitate oxidation
in skeletal muscle tissue (Figure 3.1B). Nothing else significant

42
Table 3.1: Anthropometric and Clinical Characteristics of Clinical Studies. BMI, Body Mass
Index; FM, Fat Mass; FFM, Fat-Free Mass; SAT, subcutaneous adipose tissue; VAT, visceral
adipose network; GDR, Glucose Removal Rate; EMBS, Estimated Average Body Size (FFM +
17.7); FFA, Free Fatty Acids
Anthropometry
C h a r a c t e r i s t i c (Installment-installment ± SD)
N 29
Age 26.8 ± 5.4
Weight (kg) 81.9 ± 10.3
BMI (kg/m2) 25.5 ± 2.3
Fat % 19.4 ± 4.9
FM (kg) 16.0 ± 4.8
FFM (kg) 65.9 ± 7.3
SAT (kg) 4.1 ± 1.5
VAT (kg) 0,58 ± 0,49
% Fiber Type-1 (vastus
lateralis) 35.0 ± 13.5
% Serat Tipe-2a (vastus
lateralis) 53.0 ± 14.3
% Fiber Type-2x (vastus
lateralis) 12.0 ± 10.9
M e t a b o l i c C h a r a c t e r i s t i c s

43
24-hour Respiratory Intelligence 0,89 ± 0,02
GDR (mg/min/EMBS) 11,51 ± 2,54
S e r u m s i z e
Glukosa (mg/dL)
91.0 ± 6.7
Insulin (μU/mL)
5.4 ± 4.0
FFA (nmol/L)
0,26 ± 0,08
Trigliserida (mg/dL)
87 ± 42
Kolesterol Total (mg/dL)
171 ± 25
HDL-C (mg/dL)
55 ± 12
LDL-C (mg/dL)
99 ± 23
Kolesterol/HDL
3,27 ± 0,96
HDL/LDL
0,59 ± 0,20

44
correlation between PLIN3 protein content and other clinical variables: GDR (r = 0.14, p = 0.51),
Type-I fiber (r = -0.32, p = 0.11), body weight (r = -0.12, p = 0.57), fat-free mass (r = -0.09, p =
0.64), fat mass (r = -0.06, p = 0.77), percent body fat (r = -0.02, p = 0.91), visceral adipose tissue
(r = 0.12, p = 0.59), and subcutaneous adipose tissue (r = 0.13, p = 0.53). Knockdown of PLIN3
in myotubes from sedentary thin donors revealed a ~85% reduction in complete oleic oxidation
when compared to control and siSCR (Figure 3.1D). Figure 3.1C provides a representative
immunodeficiency showing knockdown of PLIN3 in the myotube of a lean donor.
3.3.2 Differential expression and response of PLIN3 and intracellular transport proteins after
treatment of PFIs in myotubes of active, lean, and T2D.
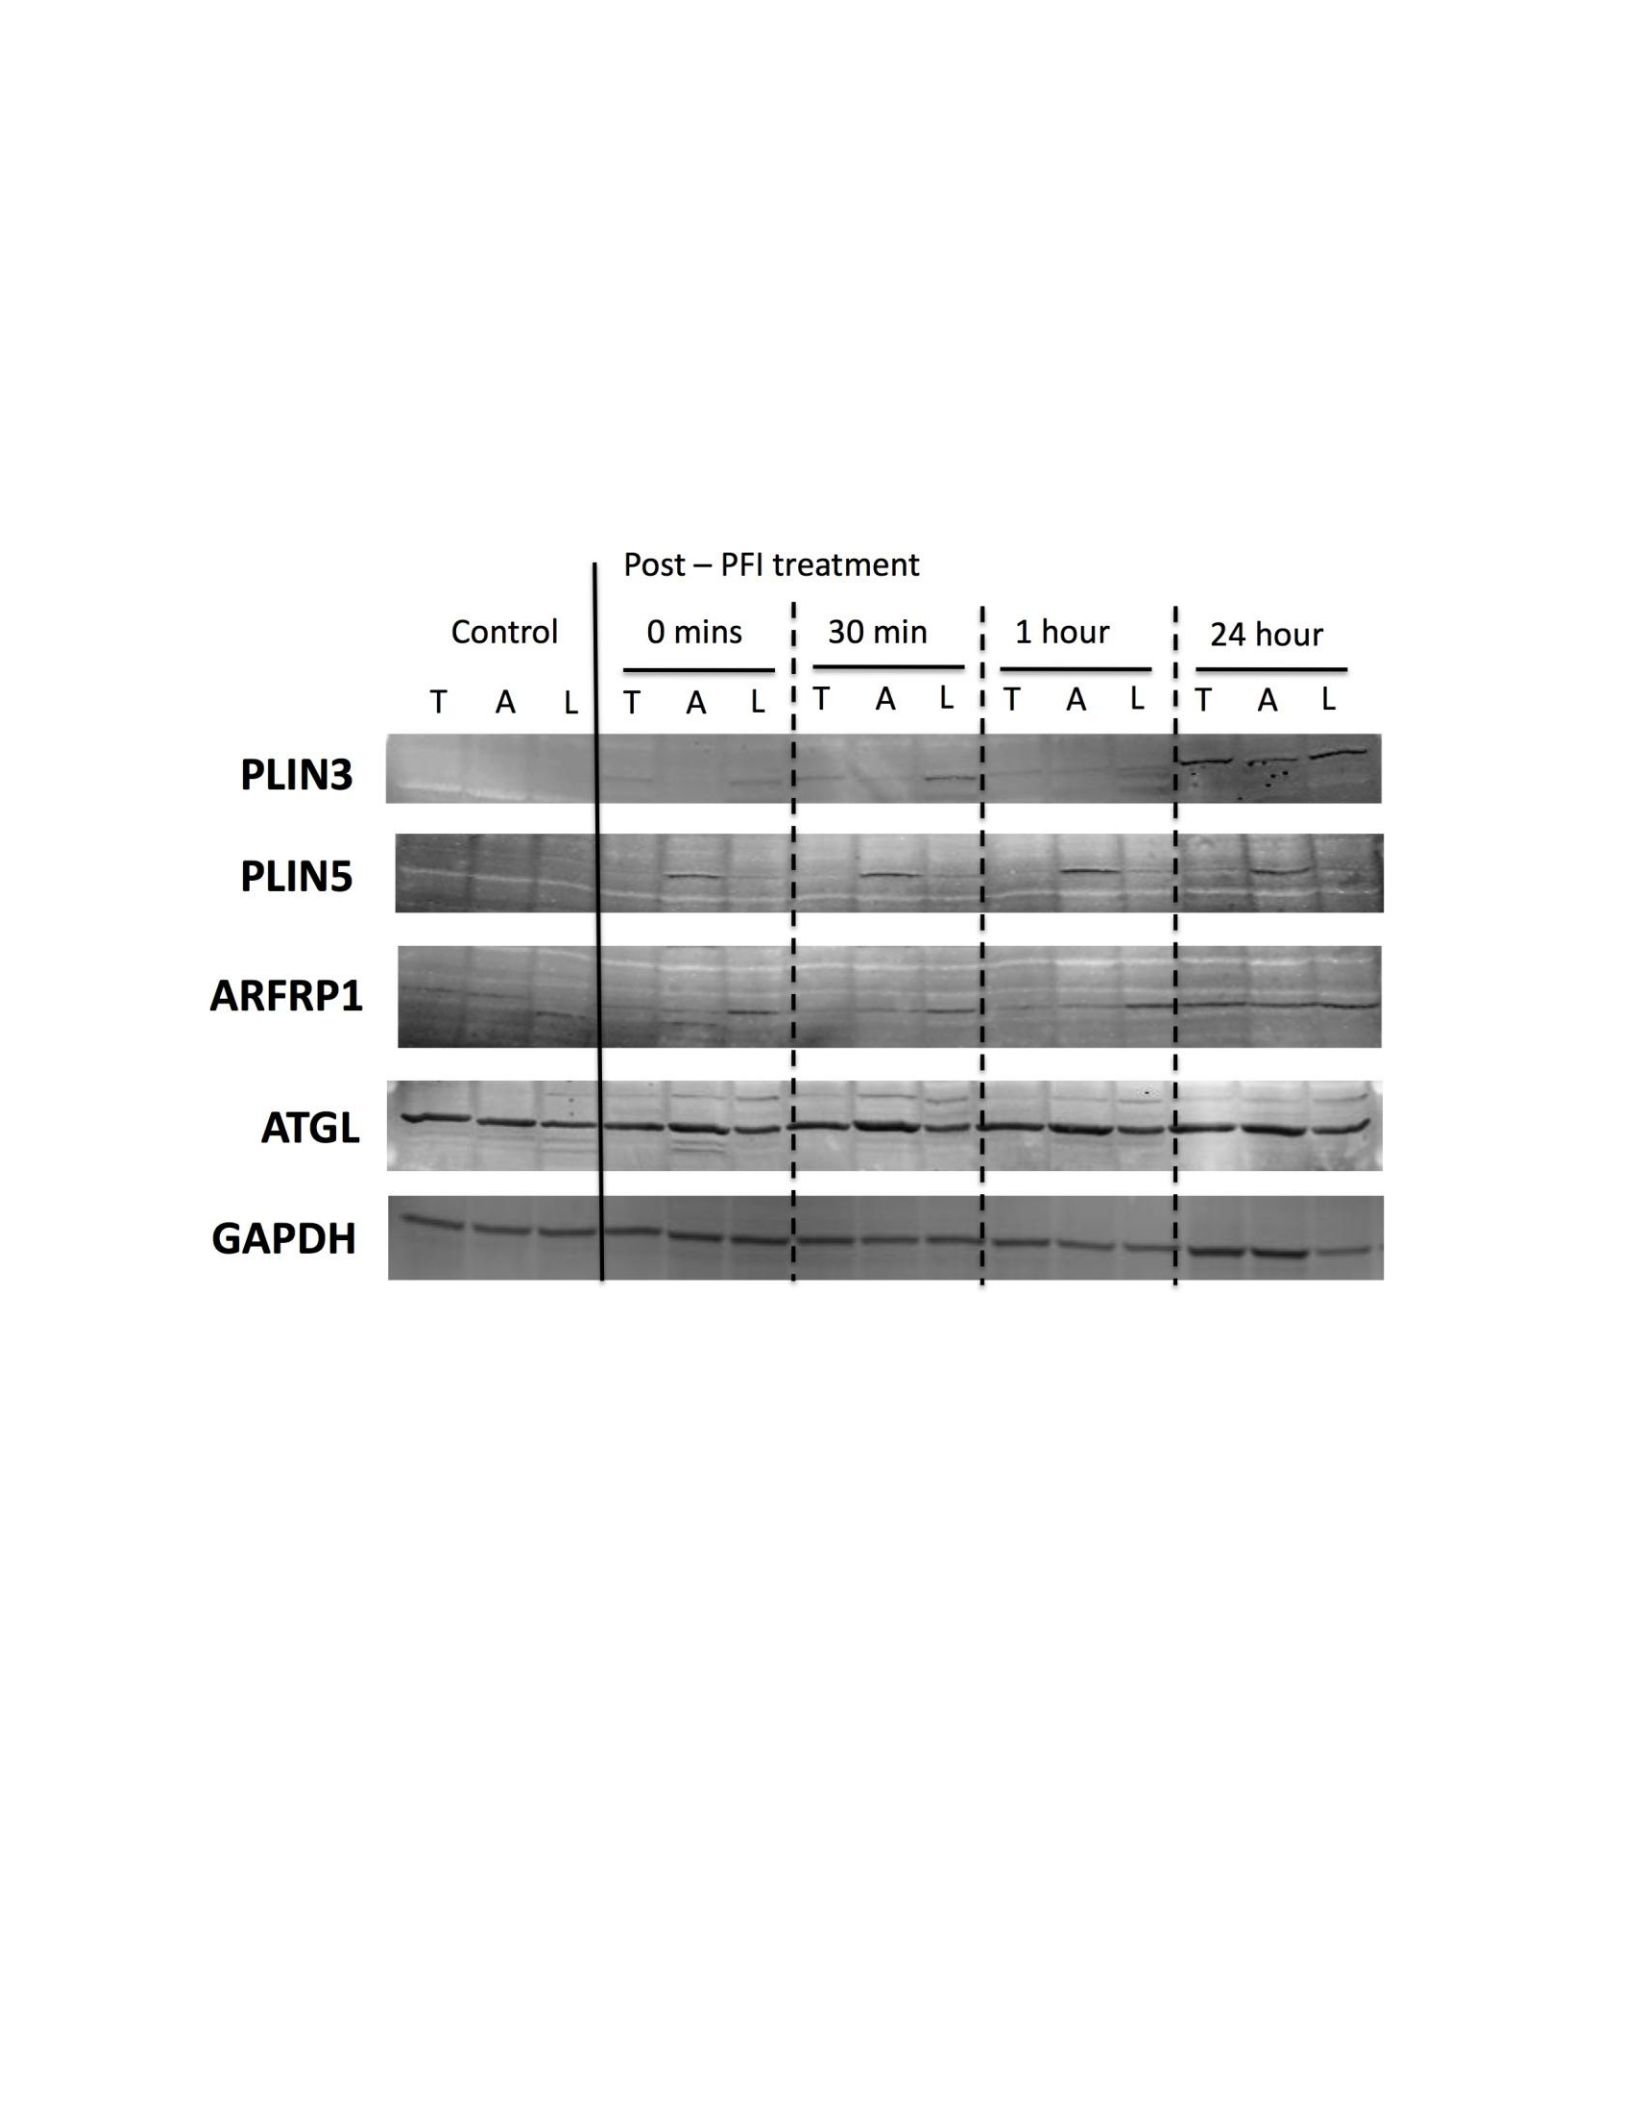
In terms of PLIN3 protein content, lean cells expressed an increase in PLIN3 after PFI
treatment and up to 24 hours after PFI treatment, similar to our previous experiment [72], while
T2D myotubes continued to increase levels of PLIN3 protein content for up to 24 hours (Figure
3.2), both expressing higher levels than the active substance. In contrast, the protein content of
PLIN5 was regulated in the active ingredient from immediately after PFI treatment to 24 hours
thereafter (Figure 3.2). Lean myotube and T2D showed almost no PLIN5 protein content with PFI
treatment (Figure 3.2).
ARFRP1 has the most prominent protein content after PFI treatment on lean above T2D and active
(Figure 3.2). ATGL levels increased in active myotubes after PFI treatment up to 1 hour time
point, with an increase in lean myotubes only at 1 hour and 24 hours post-treatment of PFI, and
almost no change in T2D myotubes (Figure 3.2). At 24 hours post-treatment with PFI, PLIN3 and
ARFRP1 had higher protein content in lean myotubes and T2D (Figure 3.2); PLIN5, however, is
strongly expressed only in the active myotube 24 h after PFI treatment (Figure 3.2).
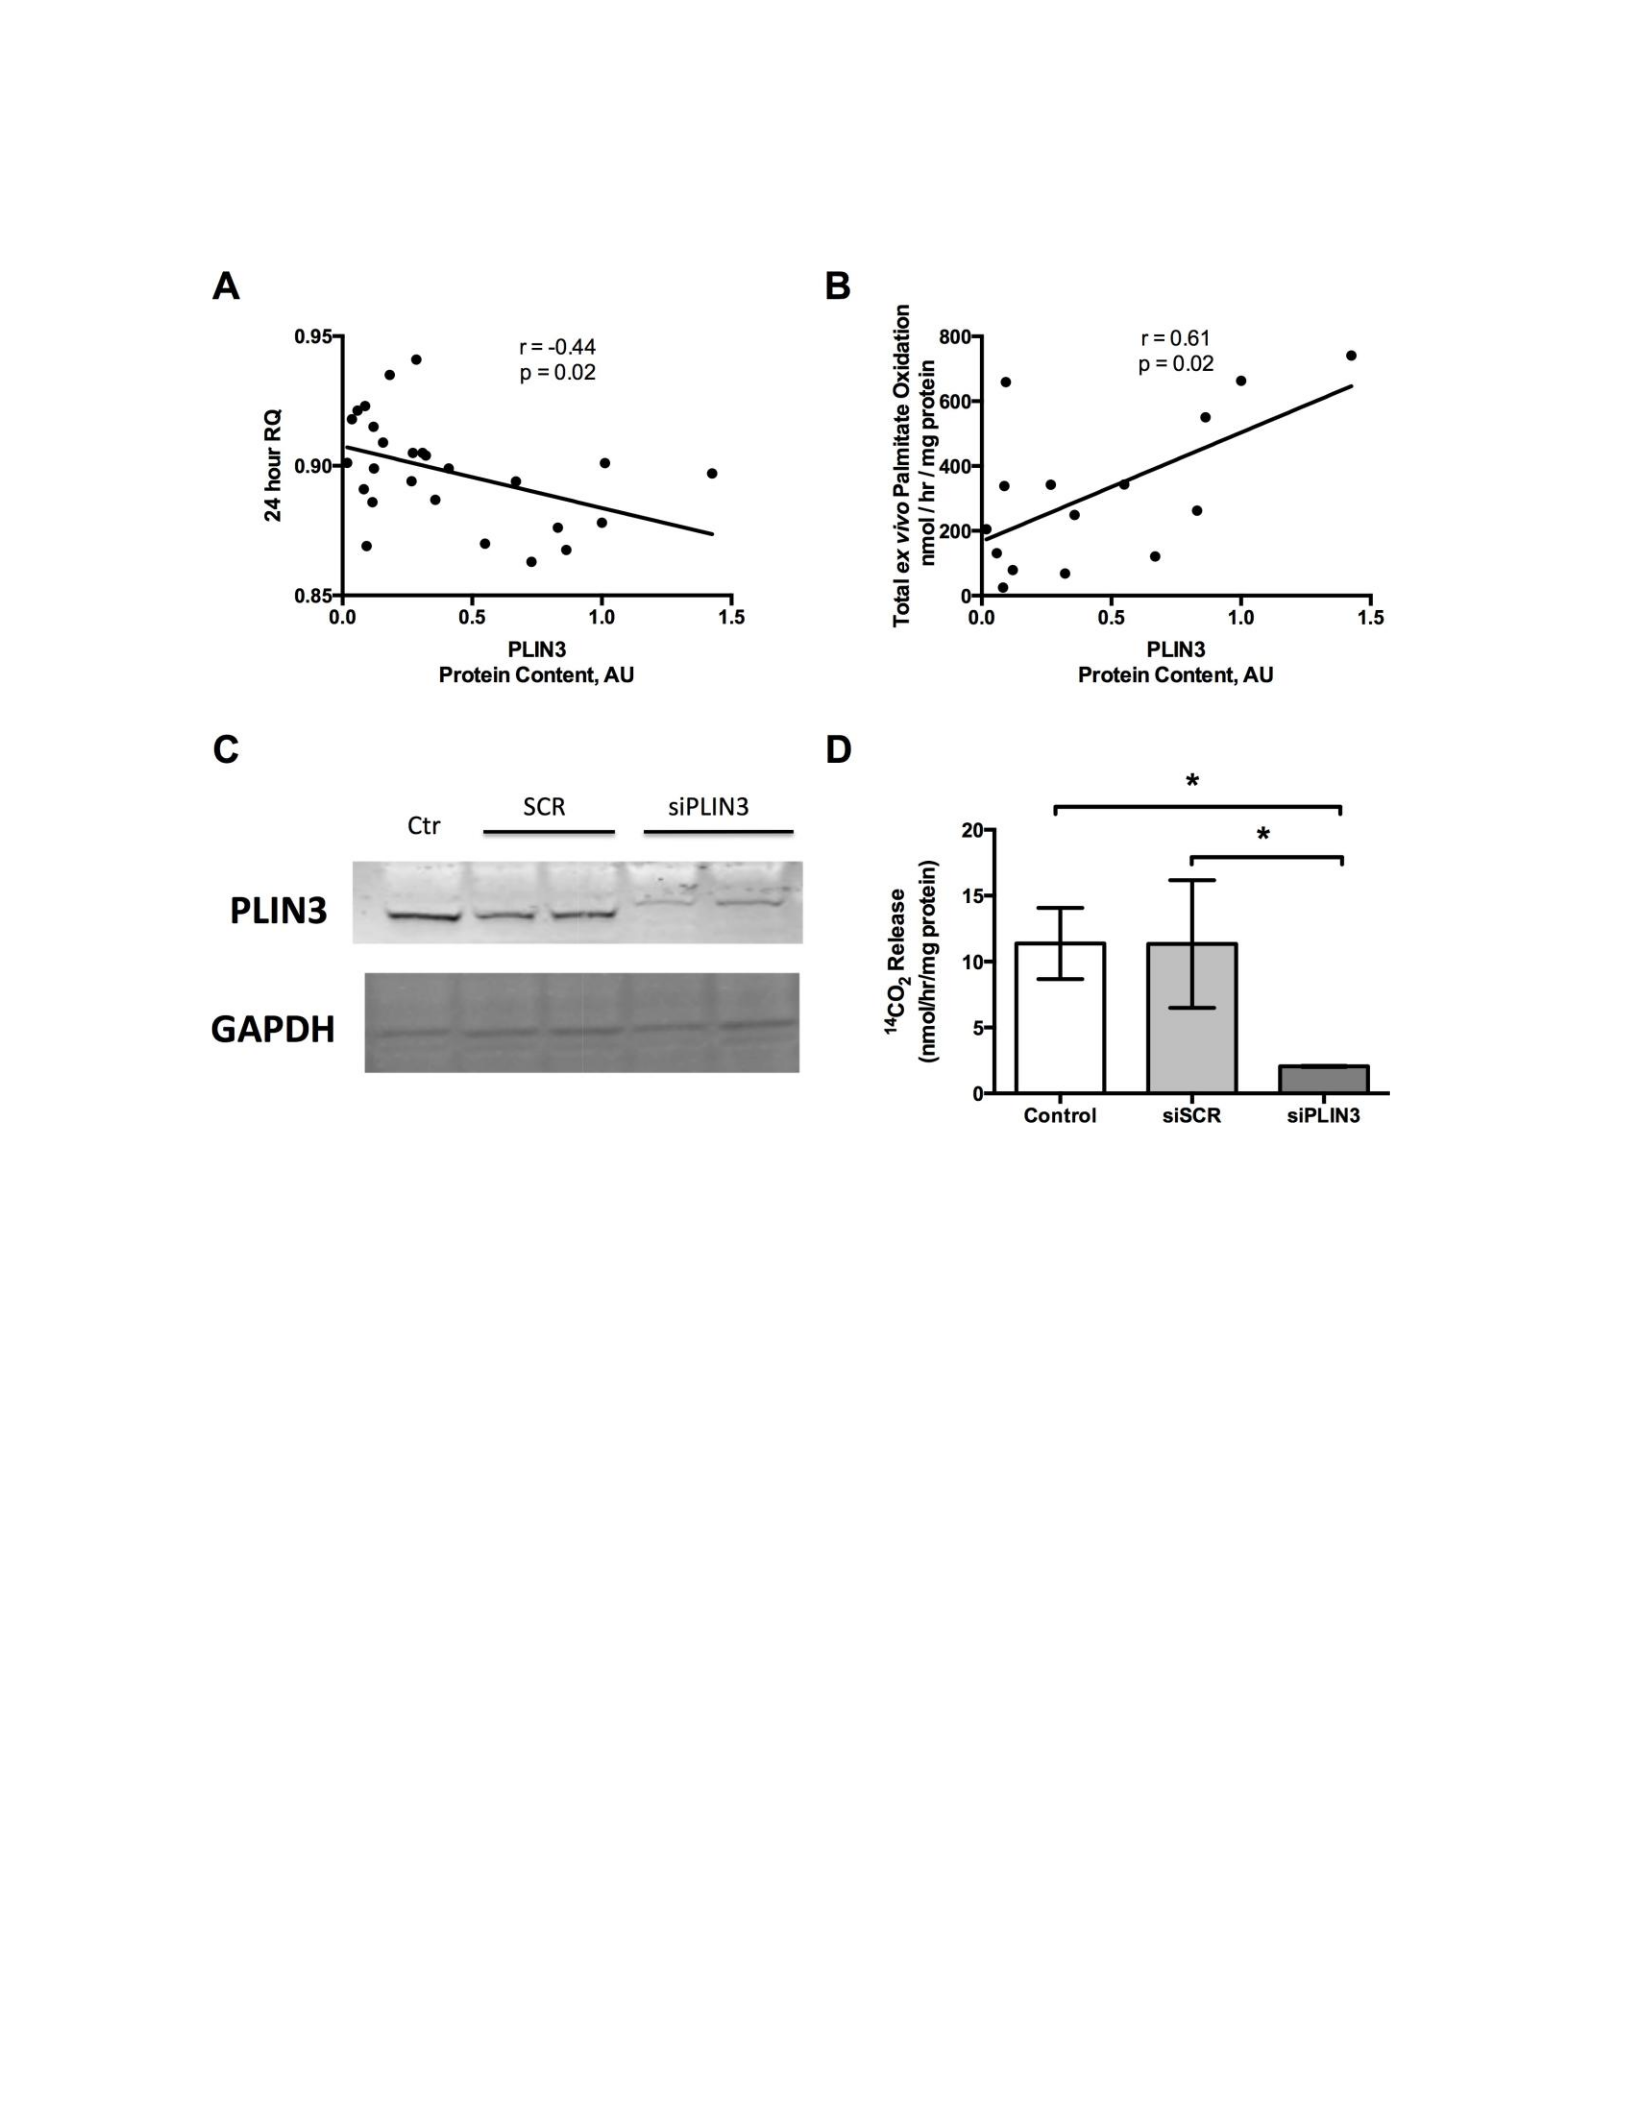
45
Figure 3.1: Correlation between resting muscle protein content of PLIN3 with whole-body
in vivo and ex vivo and muscle-specific lipid oxidation and lipid oxidation in knockdown
siRNA myotubes PLIN3. A) The PLIN3 protein content of vastus lateralis was inversely
proportional to the 24-hour respiratory intelligence (RQ) which showed that the increased PLIN3
protein content was associated with increased whole-body fat oxidation (People r = -0.44, p =
0.02, n = 26). B) The PLIN3 protein content of vastus lateralis was positively associated with the
oxidation of ex vivo palmitate from muscle tissue from vastus lateralis which showed that the
increased protein content of PLIN3 was associated with increased oxidation of skeletal muscle-
specific fat (Pearson r = 0.61, p = 0.02, n = 15). C) Representative image of western stain examined
for PLIN3 of primary human myotubes of lean and sedentary individuals under control conditions,
46
after random siRNA treatment, and after knockdown of PLIN3 siRNAs. D) Complete lipid
oxidation rate in myotubes formed from lean participants after PLIN3 knockdown compared to
control and treatment with scramble siRNA (SCR). A clear decrease in lipid oxidation was noted
in lean cells after PLIN3 knockdown. The data represent the average SEM ± of the experiments
conducted in triplicate. *p<0.05 vs. control and vs. SCR
Figure 3.2: Protein expression after lipolysis stimulation with PFI in myotubes from
active, sedentary, and type 2 diabetic donors. Primary myotubes taken from participants with
active diabetes (A); sedentary, lean (L); and type 2 diabetes (T or T2D) showed differential
protein content after PFI treatment (time travel from immediately after 3 days of PFI treatment
to 24 hours after PFI treatment).
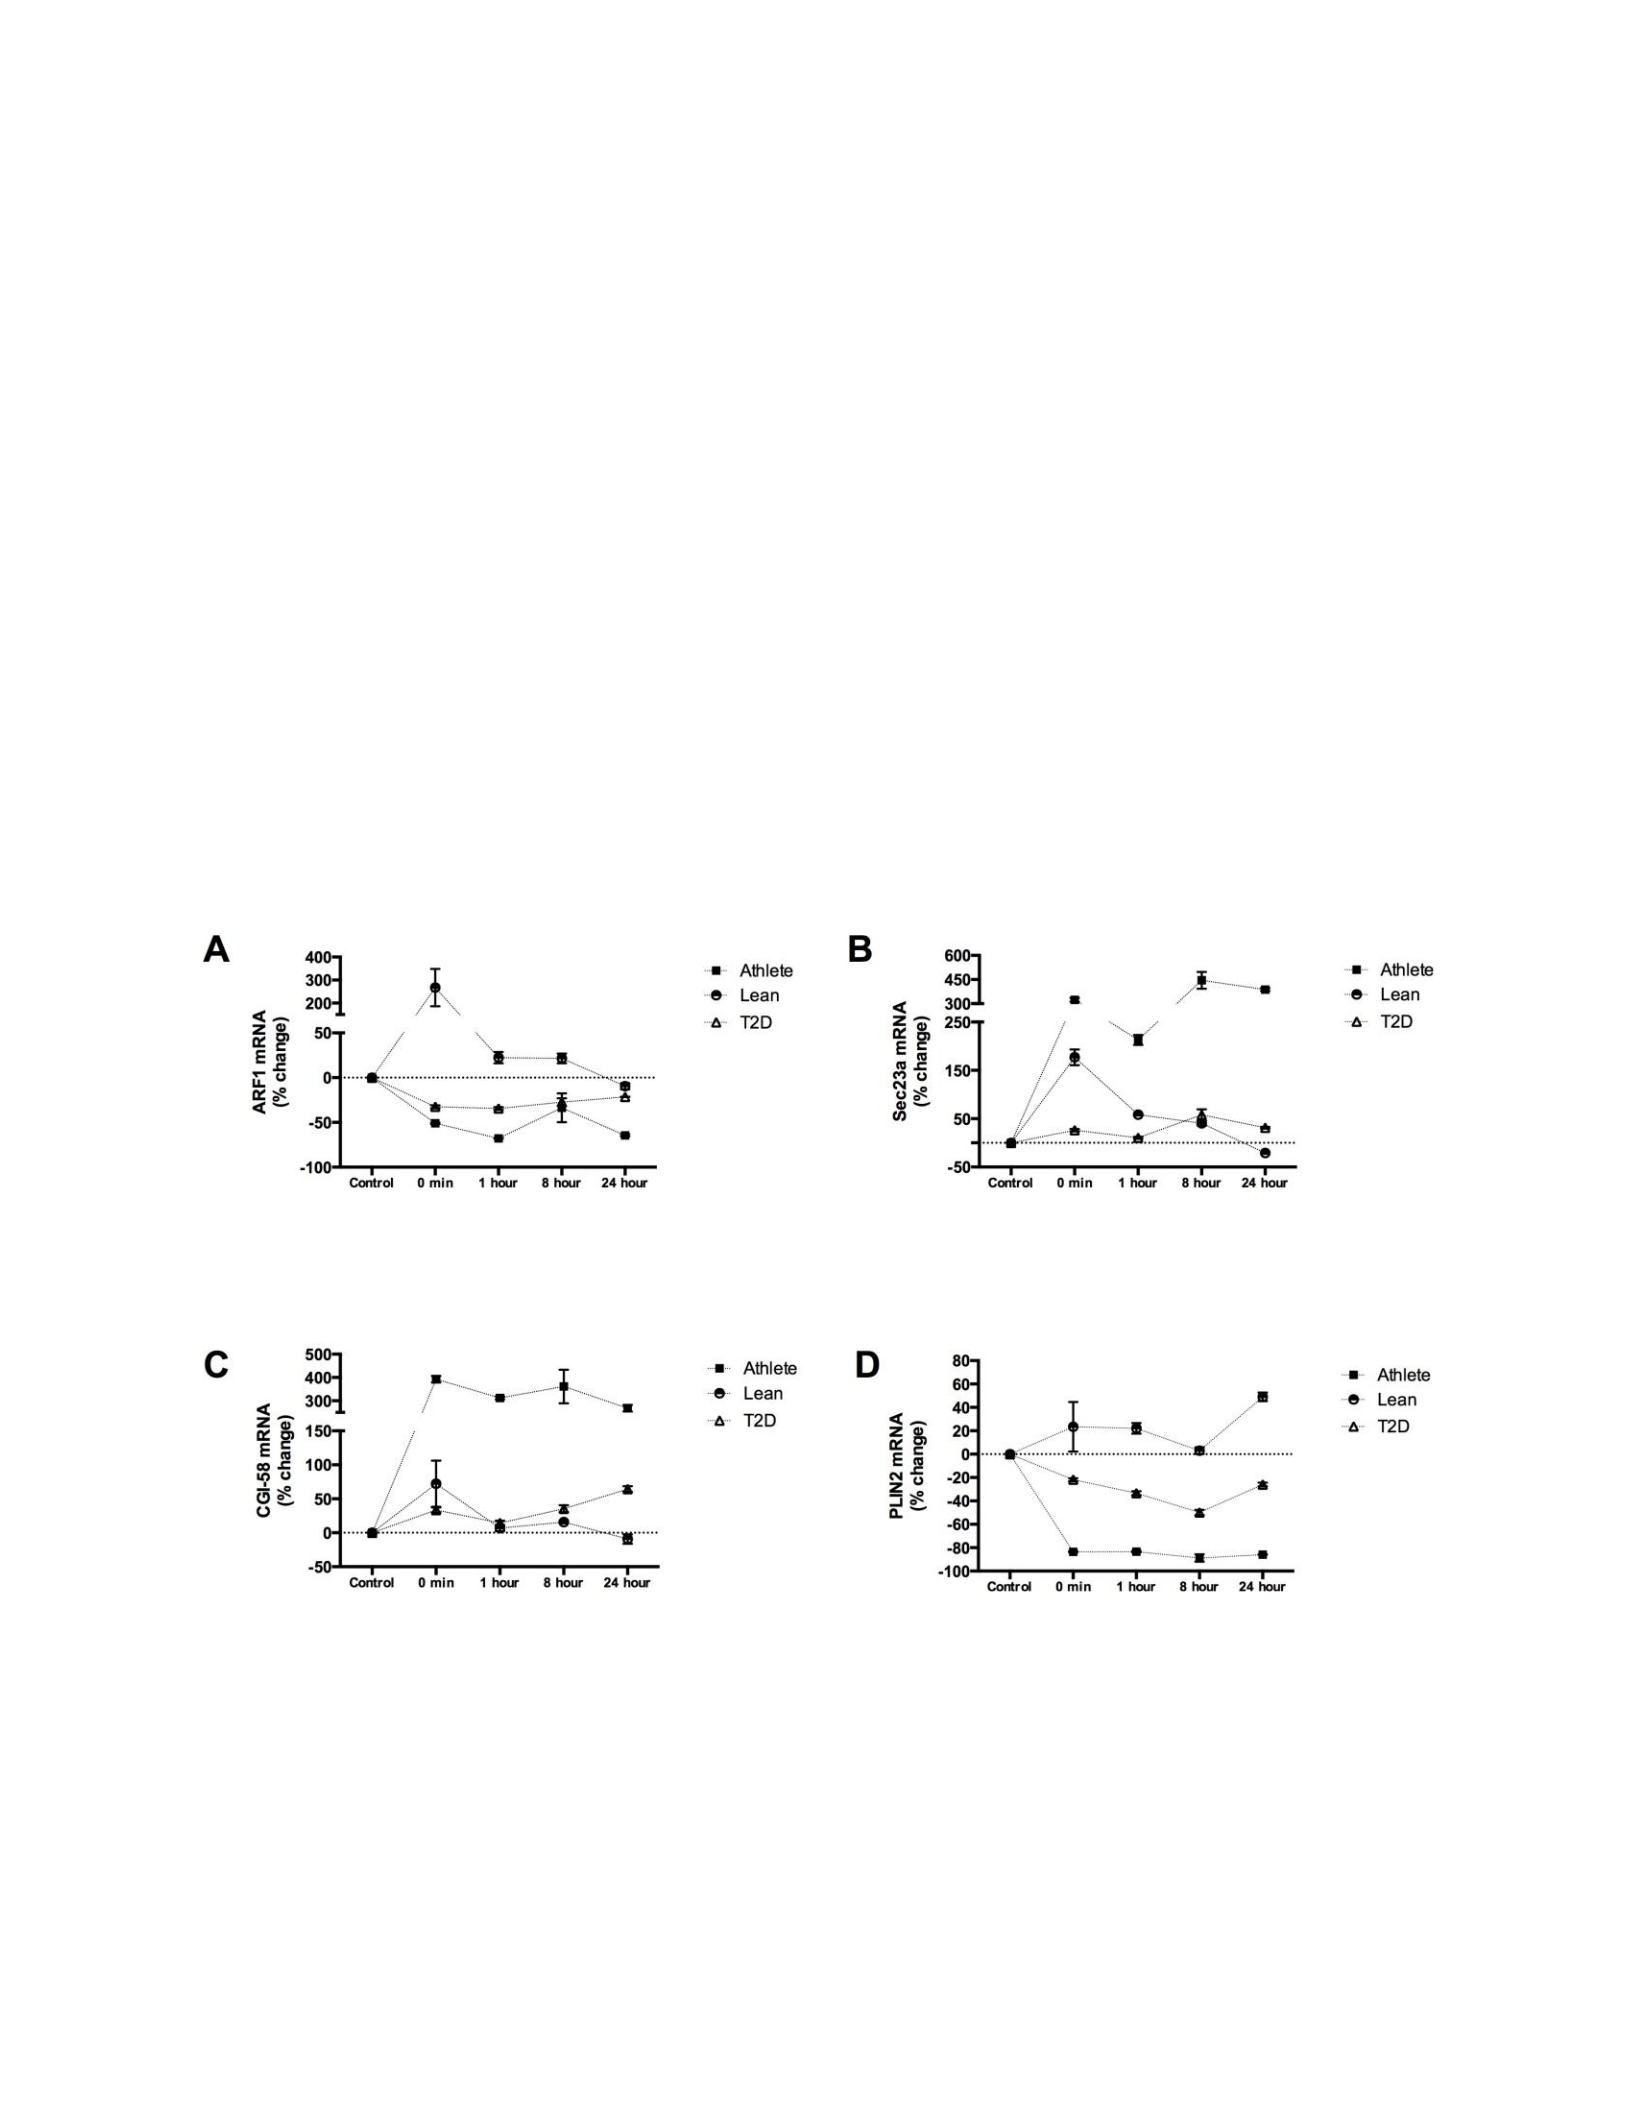
Expression of mRNA ARF1, a coatomic protein that interacts with GBF1 to facilitate
47
intracellular transport [80], increased above control conditions after PFI treatment only in lean
myotubes, while T2D and active cells decreased their ARF1 expression, especially the active
substance that reduced its expression more than T2D (Figure 3.3A). Sec23a, a complex subunit
of COPII responsible for retrograde transport of Golgi-to-ER [81], has increased expression in
lean and active myotubes after PFI treatment, while it has only increased minimally in T2D cells
(Figure 3.3B). CGI-58, an ATGL coactivator [82], increases roughly in active myotubes after
treatment with PFI over and over T2D and lean myotubes (Figure 3.3C). Finally, PLIN2, the
perilipin protein formerly known as ADRP, experienced a drastic decline The expression of
mRNA in the active myotube was followed by T2D after PFI treatment, while the cells of the lean
increased the expression of PLIN2 (Figure 3.3D).
Figure 3.3: Differential mRNA expression after PFI (time travel) treatment of myotubes
collected from active substances, leans, and T2D. A) ARF1, a coatomic protein associated with
ER-to-Golgi transport, was highly expressed in cells from lean after PFI with the active ingredient
showed the highest decrease. B) Sec23a, part of the COPII complex, was expressed differently in

48
three cohorts with the active substance having the highest increase in expression after PFI
treatment. C) CGI-58, the co-activator of ATGL lipase, is most highly expressed in the active
ingredient after treatment with PFI. D) PLIN2, a member of the perilipin family, showed different
expression patterns among the three cohorts with a tendency to increase their expression after PFI
with the active substance having a decrease in mRNA expression of nearly ~80%, and T2D
experienced a decrease of between ~20% to ~60% after the time course of PFI post-treatment.
All experiments were performed in triplicates and were represented as the average of the SEM ±
for the percentage change.
3.3.3 Reduced lipid oxidation in vitro after treatment with brefeldin A in lean myotubes and T2D
but not on the active ingredient
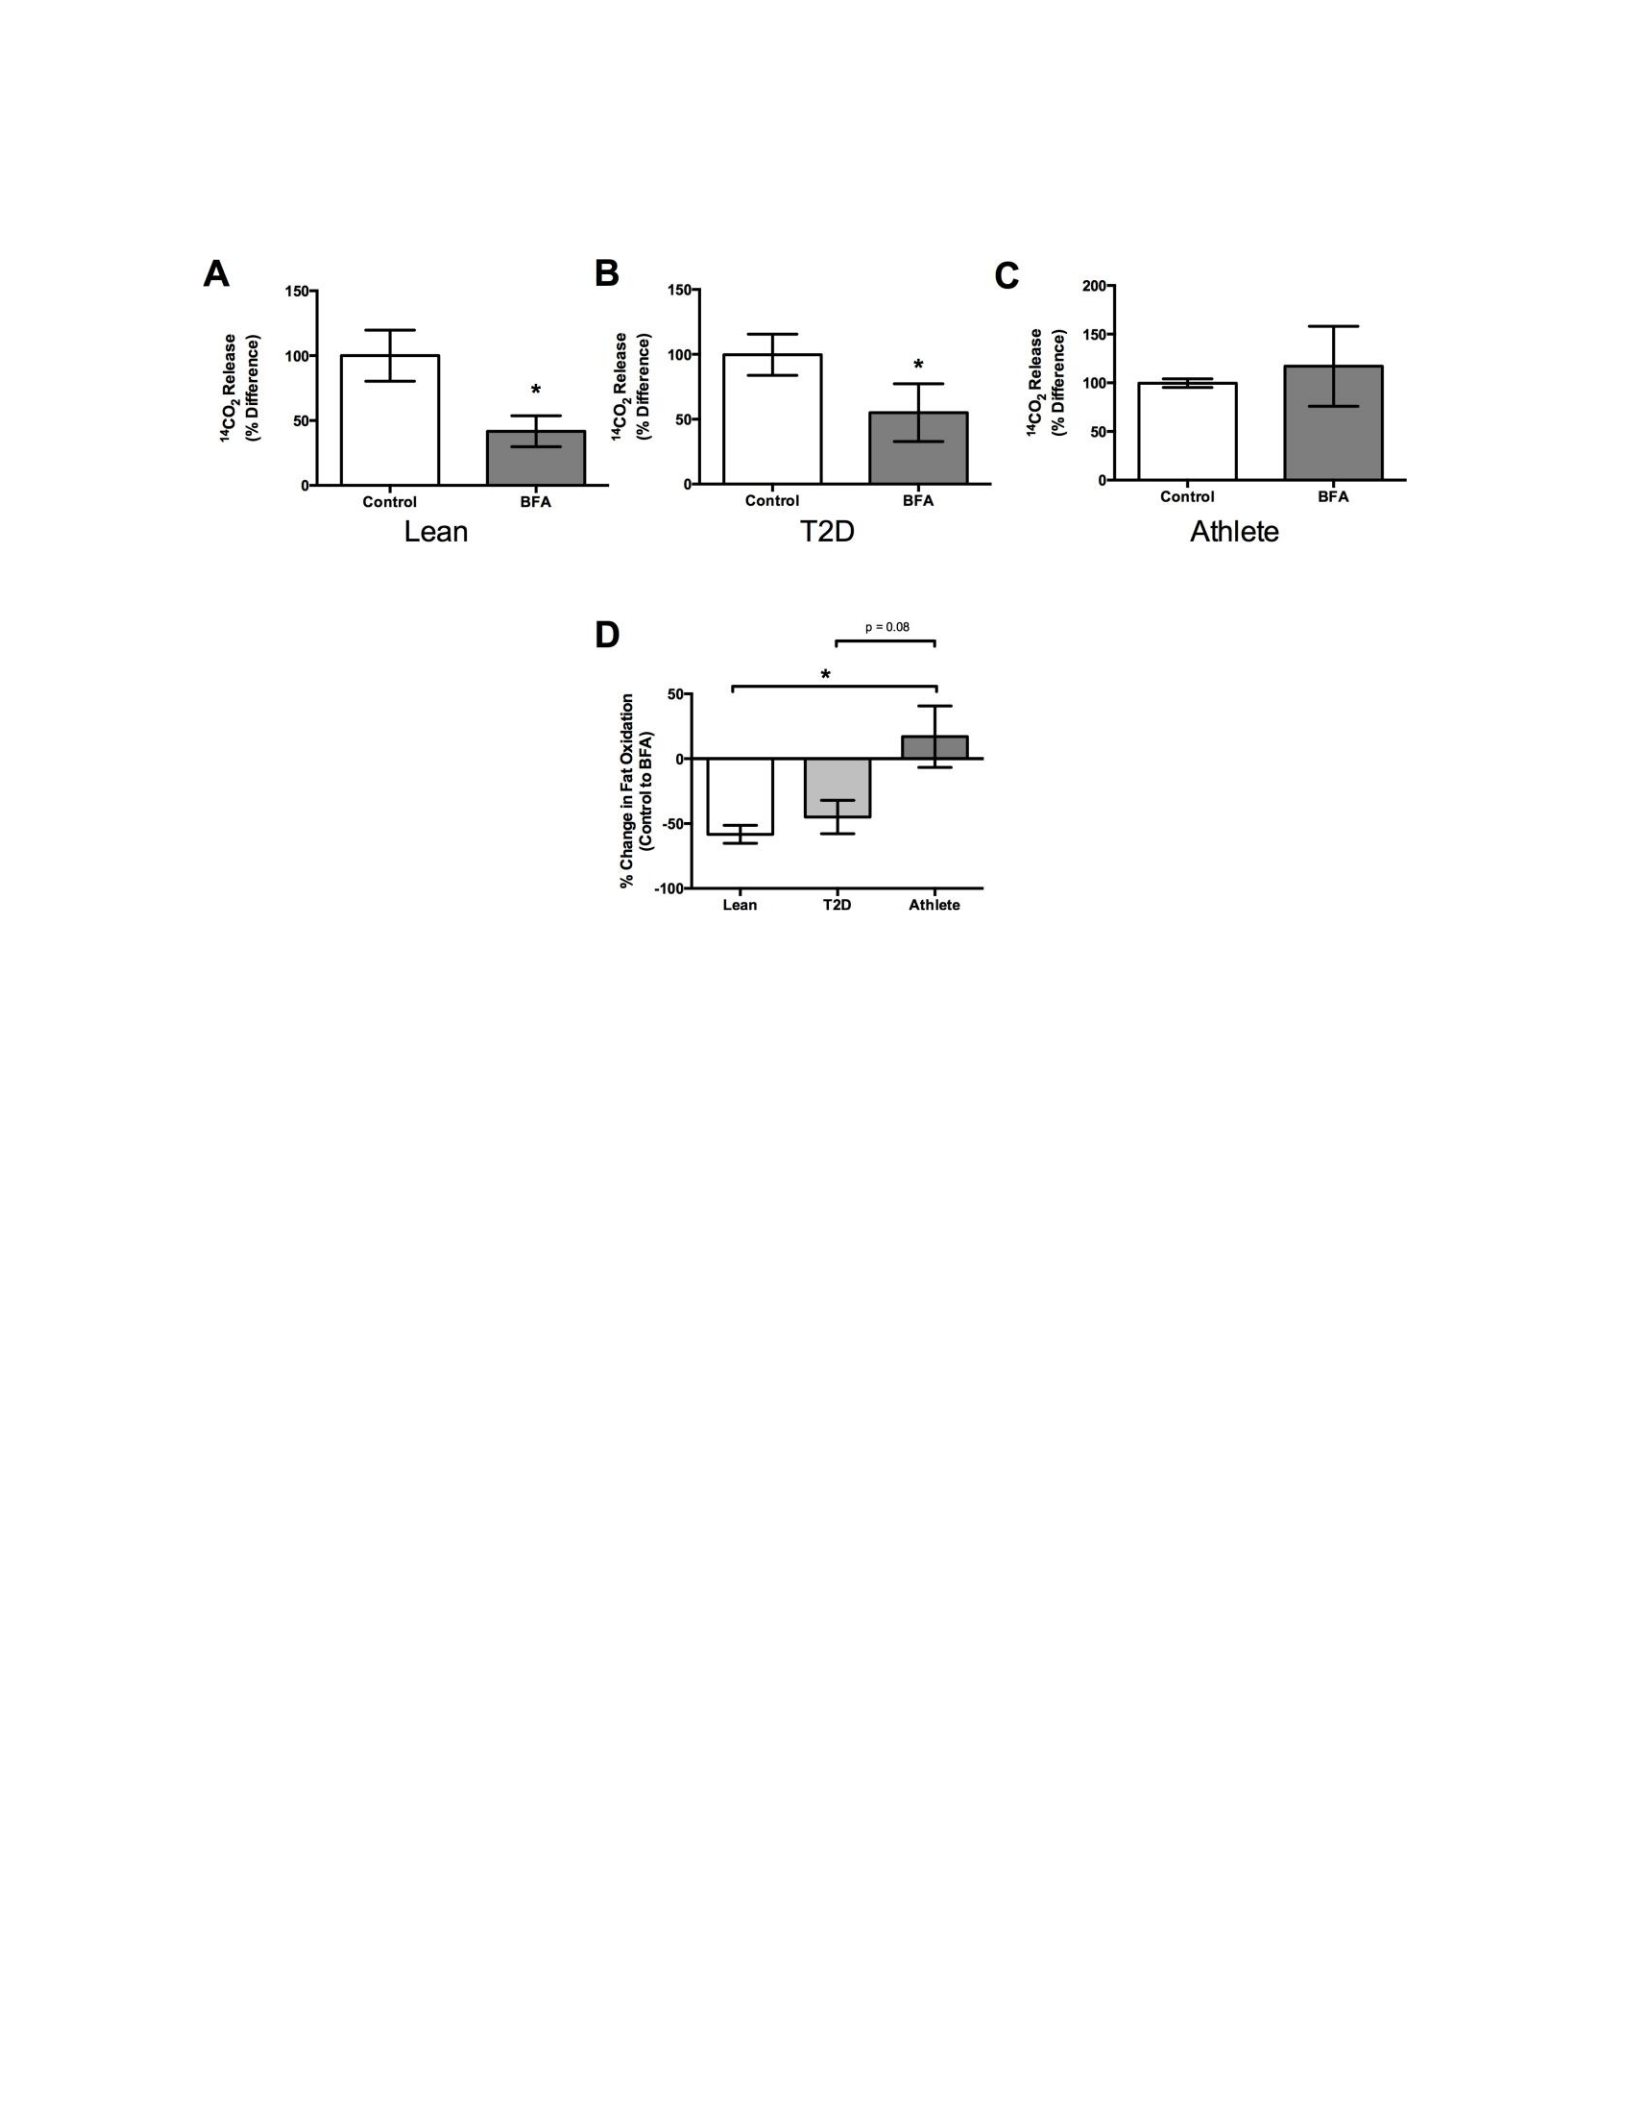
Treatment of myotubes with brefeldin A (BFA), a drug that inhibits ARF1 activity [48],
showed reduced oxidation of in vitro oleate for lean donors (Figure 3.4A) and T2D (Figure
3.4B). However, oleic oxidation was not affected after BFA treatment on active myotubes
(Figure 3.4C). The percentage of oxidation change of oleate in vitro compared to the control
conditions revealed a significant difference between cells from lean and active (p = 0.02) and
tended towards a difference between T2D and active (p = 0.08), with no difference in oxidation
between lean myotubes and T2D (Figure 3.4D).
Table 3.2: Anthropometric and Clinical Characteristics of Primary Myotubes. FM, Fat
Mass; FFM, Fat-Free Mass; BMI, Body Mass Index; GDR, Glucose Removal Rate; EMBS,
Estimated Average Body Size (FFM + 17.7). The P value is provided from a one-way ANOVA.
Tukey's post-hoc test is used to evaluate the differences between groups: a, p < 0.05 compared to
Lean; b, p < 0.05 compared to Type 2 Diabetics; c, p < 0.05 compared to Active
49
Active
Lean, Sedentary
Type 2 Diabetics
Mean ± SD
Mean ± SD
Mean ± SD
P value
N
4
5
4
--
Weight (kg)
79.98 ± 8.88
billion
76.50 ± 8.19b
110.53 ±
18.31
a,c
0.005
FM (kg)
10.58 ± 1.96
billion
14.36 ± 6.29
billion
31.41 ± 2.89
a,c
<0.001
FFM (kg)
69,75 ± 7,50
62,14 ± 4,30
64,73 ± 5,37
0.18
Fat %
13.15 ± 1.95
billion
18.36 ± 6.39
billion
35.27 ± 5.37
a,c
<0.001
BMI
25.12 ± 2.55b
24.18 ± 0.55
billion
39,65 ± 6,98
a,c
<0.001
Glukosa Serum (mg/dL)
88.75 ± 2.75
billion
87.80 ± 5.50
billion
117.25a,c
0.02
GDR (mg/min/EMBS)
12.39 ± 2.29b
11.16 ± 3.01b
1.26 ± 0.56
a,c
<0.001
Maximum ATP
production
(mM/min)
1.17 ± 0.07
a,b
0,66 ± 0,11c
0,59 ± 0,24c
<0.001
Basal ATP production
(μM/min)
7.27 ± 2.18b
5.35 ± 1.42
3.37 ± 1.81c
0.04
50
24-hour Energy
Expenditure (kcal)
3854 ± 339.79
a,b
2181 ± 132.23c
2675 ± 201.23c
<0.001
51
Figure 3.4: Oxidation of lipids in myotubes with and without brefeldin A treatment.
Complete fatty acid oxidation (CO2 release) in myotubes formed from lean (A), T2D (B), and
active substances
(C) under control conditions and after 30 minutes of treatment with brefeldin A (BFA), a drug
known to inhibit ARF1 and ER-to-Golgi transport. D) Percentage change in fatty acid oxidation
compared to control conditions between leans, T2Ds, and active substances. All data represent the
average SEM ± of the experiments performed in triplicate. *P<0.05 vs. control
3.4 Discussion
The paradox of athletes has represented a curiosity in skeletal muscle insulin resistance
research in which athletes and T2D have high IMCL, yet represent bilateral extremes across the
spectrum of insulin sensitivity. Our study has shown for the first time the expression of the

52
differential proteins perilipin 3 and perilipin 5 in the primary skeletal myotubes of active, lean and
T2D after in vitro lipolysis treatment. In addition, our study has demonstrated a novel potential
role that PLIN3 may play in facilitating lipid oxidation of skeletal muscle as evidenced by the
reduced rate of lipid oxidation in the myotube of a lean donor after a PLIN3 knockdown and its
relationship with whole-body in vivo lipid oxidation and skeletal muscle-specific ex vivo lipid
oxidation.
Previous investigations into the PAT protein family in human skeletal muscle have
focused extensively on the function of PLIN5. Repeated investigations have shown direct protein-
protein interactions between PLIN5 and ATGL [32, 33], and that overexpression of PLIN5 in
mice has increased lipid oxidation [31]. Our investigation showed that PLIN5 was highly
regulated in active donor-derived myotubes after stimulation with palmitate, forskoline, and
ionomycin (PFI) which had previously been shown to increase lipid oxidation and was referred to
as "sports mimetics" (Figure 3.2) [60]. Our findings support the hypothesis that skeletal muscle
of the active ingredient trained resistance uses PLIN5 for lipid droplet packaging for faster lipid
oxidation as it may be due in part to the direct interaction between PLIN5 and ATGL, which has
been shown previously [32, 33]. As we show in Figure 3.2, ATGL is more acutely responsive to
PFI treatment in active myotubes, and likewise, CGI-58, an ATGL co-activator, greatly increases
mRNA expression in active myotubes over and over sedentary, lean myotubes and T2D myotubes
after PFI treatment (Figure 3.3C). In addition, it has been proven that PLIN5 packs lipid droplets
that are exclusively composed of triacylglycerides (TAG) [34]. We have previously shown that
primary myotubes from active donors have significantly increased TAG levels during lean and
T2D [16], thus providing an additional explanation for the increased PLIN5 levels in the active
substance after the lipopolitical stimulus.
However, the abundance of data on PLIN5 and its relationship to lipid oxidation may have

53
overshadowed other targets that may be relevant to muscle lipid storage for oxidation. PLIN3 has
been shown, in our previous study, to be positively associated with Both skeletal muscle tissue fat
oxidation in vivo and ex vivo throughout the body after resistance training in twenty healthy men
[72]. We also showed an increase in PLIN3 protein after epinephrine stimulation in primary human
myotubes [72]. Previous investigations have shown the colocalization of ATGL to PLIN3-coated
lipid droplets in HeLa cells [44, 45], and the colocalization of PLIN3 to lipid droplets in isolated
mouse skeletal muscle [43]. All of this has provided indirect evidence of PLIN3's involvement
with the facilitation of lipid oxidation in skeletal muscle. Our current study independently repeats
our findings on the protein content of PLIN3 associated with whole-body and skeletal muscle-
specific ex vivo lipid oxidation;this time, though, it used a 24-hour metabolic chamber (Figure
3.1A) and used skeletal muscles taken in both resting and basal conditions (Figure 3.1B).
Importantly, our study with human myotubes also showed a strong reduction in lipid oxidation
after knockdown of PLIN3 (Figures 3.1C and 3.1D). Previously, we have reported that in the
naturally occurring knockdown of PLIN3 protein in primary adipose cultures taken from women
with polycystic ovary syndrome (PCOS), fat oxidation decreased, but increased after aerobic
exercise, which was concurrently associated with increased PLIN3 protein content [83]. Here, we
show that the knockdown induction of PLIN3 protein content also results in a reduction in fat
oxidation. This evidence suggests a significant possibility that PLIN3 serves as a target responsible
for facilitating lipid oxidation in sedentary, emaciated individuals and in insulin-resistant
individuals. We further investigated whether the effect of exercise mimetic stimulation on PLIN3
and PLIN5 protein content on active, thin, and T2D donors. Our findings show remarkable
differences in PLIN3 and PLIN5 responses to exercise mimetic stimulation between these three
groups. The active substance almost exclusively expresses PLIN5 after exercise stimulation
(Figure 3.2C)

54
while lean and T2D support PLIN3 expression (Figure 3.2B). In addition, we investigated the
expression of ER-to-Golgi transport coatomer GTPase. Previous investigations in HeLa cells have
suggested a dependence of the coatomeric protein in facilitating the delivery of ATGL to PLIN3-
coated lipid droplets [47, 71]. We previously reported an increase in the regulation of several
coatomeric factors after long resistance training in human skeletal muscle tissue [72]. We have
also previously reported the same phenomenon occurring in adipose tissue from women with
PCOS, a cohort that seems to support PLIN3 expression after aerobic exercise [83]. Here, we have
demonstrated the differential response of coatomeric targets among cells from active, lean and
T2D after in vitro lipopolitical stimulus at the protein level (ARFRP1, Figure 3.2) and mRNA
levels (ARF1 and Sec23a, Figure 3.3). In addition, we showed differences in related targets
involved in lipid packaging and lipolysis among these populations (CGI-58 and PLIN2, Figure
3.3). Although these differences are new, they themselves are not fully insightful. Thus, we further
investigated the lipid oxidation rate in cultured primary myotubes of these three cohorts after
treatment with brefeldin A (BFA), an inhibitor of ARF1 activity [48]. BFA has previously been
shown to block ATGL delivery to PLIN3-coated lipid droplets [47], but has also been shown not
to inhibit intracellular transport of PLIN3 [84]. We showed a reduction in lipid oxidation in
myotubes from lean donors and in T2D donors after BFA treatment; therefore, it suggests that
lipid oxidation is partly dependent on coatomeric GTPases in these two groups (Figures 3.4A and
3.4B). On the other hand, myotubes from active donors showed no reduction in lipid oxidation,
exhibiting a distinct divergent pathway that does not require coatomic GTPase to facilitate lipid
oxidation (Figure 3.4C). The novelty of this aspect of our research is the demonstration of
differential upregulation of PLIN3 and PLIN5 after mimetic exercises

55
stimulation, differential expression of coatomic GTPases, and differential lipid oxidation rates
after BFA treatment. These data suggest the possibility of a previously unexplored lipid oxidation
pathway relying on PLIN3 and coatomer GTPase that is easier to use in sedentary, lean and
possibly T2D skeletal muscle compared to the active substance.
In addition, these data highlight that PLIN3 would be a pharmacological target in individuals with
T2D due to the fact that they seem to favor the expression of lipopolitically-induced PLIN3 and
do not seem to express PLIN5 much.
One of the main strengths of our study is the fact that we independently reproduced the
positive correlation association between the whole body in vivo using the results of 24-hour
metabolic chamber and lipid oxidation ex vivo skeletal muscle with PLIN3 protein content. This
showed that in two independent studies separate from inactivity that the expression of skeletal
muscle PLIN3 was associated with lipid oxidation [72]. To further reinforce these results, we
managed to lower the expression of PLIN3 protein in primary human myotubes collected from
individuals, who participated in the reported clinical investigation, and showed that in vitro lipid
oxidation was reduced with reduced PLIN3 protein content. The second major strength of our
study is the fact that our next data presented here was exclusively performed on human primary
myotubes, as opposed to cultured cell lines. We and others have shown that human myotubes
reflect donor phenotypes [16, 49], thus allowing a powerful tool to investigate the
pathophysiology of skeletal muscles associated with T2D by utilizing primary myotubes obtained
from donors with T2D. Although there is no substitute for rigorous clinical investigation of
skeletal muscle tissue directly in this cohort, we argue that our experiments

56
in the primary human myotube offers conclusive insights into PLIN3 as facilitating the
oxidation of muscle lipids.
The T2D participants we were able to recruit for this study were taking medications that
help regulate hyperglycemia (e.g. metformin, sulfonylurea, and insulin). Therefore, the effect of
treatment on differences in outcomes from T2D participants cannot be completely ruled out. We
acknowledge that the inclusion of obesity, non-diabetic cohorts as well as non-drug T2D subjects
may provide further insight into our results.
However, based on the fact that our goal is to explore the effects of lipolimic stimulation on PLIN3
content and inhibition of coatomic function at the level of lipolysis in the myotubes of the three
cohorts to see if there is actually a difference, our data presented here are very important.
To conclude, the expression of perilipin 3 skeletal muscle is associated with in vivo and
ex vivo lipid oxidation, and has been shown to be a target for the facilitation of lipid oxidation in
primary human myotubes taken from healthy, thin, sedentary male donors. PLIN3 was more
regulated higher on myotubes taken from lean and T2D donors after mimetic stimulation of in
vitro exercise. The coatomic target of ER-to-Golgi ARF1 also appears to be involved by
facilitating lipid oxidation in the primary myotubes of lean and T2D donors. In contrast, primary
myotubes from active donors did not appear to express PLIN3 much, but rather expressed PLIN5,
after in vitro lipopolitical stimulation. In addition, active donors did not appear to rely on ARF1
or related coatomer proteins to stimulate lipid oxidation whereas sedentary patients and patients
with type 2 diabetes did. These data suggest the potential of two separate pathways (PLIN3 and
PLIN5) in lipid oxidation regulation in skeletal muscle that may depend on

57
individual training status, and thus can partly offer insight into the paradoxical existence of
athletes.

58
CHAPTER 4: POTENTIAL EFFECTS OF AEROBIC EXERCISE ON PERILIPIN 3
EXPRESSION IN ADIPOSE TISSUE OF WOMEN WITH POLYCYSTIC OVARY
SYNDROME: A PERCONTOH3 STUDY
4.1 Introduction
Polycystic Ovary Syndrome (PCOS) is a complex endocrine and reproductive disorder
that affects about 4–7% of women of reproductive age [2, 3]. As the main cause of infertility in
women of reproductive age, PCOS is characterized by the presence of menstrual disterbances,
hyperandrogenemia, and ovarian cysts [85]. Similarly, about 70% of women with PCOS
experience increased adiposity [6], and between 20–43% have reduced insulin resistance and
glucose control [4, 5]. One possible cause speculated to contribute to this irregular metabolic
phenomenon is a defect in adipose tissue [86].
The adipose tissue serves as a storage reservoir for excess lipids, a reserve that must be
easily insured on increased energy demand. The inefficient ability of adipose tissue to mobilize
and secrete free fatty acids during energy demand conditions has been associated with impaired
glucose tolerance and type 2 diabetes [87-89]. It has previously been documented that women
with PCOS have dysfunction in catecholamine-mediated lipase and lipolysis activity [90-92]. It
has subsequently been reported that testosterone can reduce: 1) catecholamine-stimulated adipose
tissue lipolysis [93, 94]; 2) expression of beta-adrenergic receptors in adipose tissue [93, 94], and
3) adrenergic-stimulated lipolysis in brown adipose tissue [95]. Possible molecular targets, such
as lipase expression, have been involved

59
as a factor regulated by testosterone [94, 96, 97], thus offering a possible link between lipolysis
disorders and the hyperandrogenic state seen in women with PCOS.
Exercise has been shown to improve some of the metabolic disorders typical of PCOS [98-100],
and has been shown to increase adipose tissue lipolysis [101, 102]. Previous studies from our
group revealed an increase in basal and pharmacological lipolysis stimulated with isoproterenol
from adipose tissue after exercise [103]. The molecular markers that regulate lipolysis in adipose
tissue of women with PCOS, however, have not been thoroughly studied.
Previous investigations have shown that a single nucleotide polymorphism in the perilipin
gene (PLIN1) present in women with PCOS is associated with impaired glucose tolerance and
elevated LDL [104], possibly involving a potential role for the lipolysis family of perilipin
proteins, lipases, and related factors influencing adipose tissue lipolysis. Recent investigations
have also identified several coatomic GTPase proteins (ARF1, Sec23a, βCOP, GBF1, ARFRP1),
which are typically involved in ER-to-Golgi transport, and that are involved in the delivery of
adipose triglyceride lipase (ATGL) tissue to lipid droplets, especially lipid droplets coated by
perilipin 3 (PLIN3) [47]. We recently showed that PLIN3 and coatomic GTPase in skeletal muscle
tissue and in primary human skeletal muscle culture are associated with increased fat oxidation
after exercise and lipolysis stimulation [105]. Therefore, we hypothesize that these new lipolysis
mediators may also be expressed differently in the adipose tissue of women with PCOS, where
lipolysis is disrupted, and regulated after aerobic exercise. We investigated the expression of
lipase, perilipin, and coatomic GTPase of adipose tissue in a cross-sectional cohort of 8 women
with PCOS compared to

60
women with normal menstruation according to age, BMI, and body fat percentage. Next, in
women with PCOS, we investigated the effects of a 16-week aerobic exercise training program
on lipolysis both on adipose tissue and in stroma-derived adipose cultures. Our results demonstrate
a previously unexplored potential role for perilipin 3 (PLIN3) and coatomeric, (ADP 1 (ARF1)
ribocylation factor, ARF-related peptide 1 (ARFRP1), beta subunit coatomic complex 1 (β-
COP1), and coatomer complex 2 23a (Sec23a)) subunit in lipolysis regulation in adipose tissue.
4.2 Materials and Methods
4.2.1 Participants and study design
Eight obese women with PCOS and eight age, BMI, and fat percentage matched healthy
women with no clinical signs of abnormal menstruation or hyperandrogenemia were recruited in
this study (anthropometric characteristics are provided in Table 1). The reported results for this
investigation are an additional project to clinical studies, designed and supported to determine the
effects of aerobic exercise programs on body composition and whole-body insulin resistance in
obese women diagnosed with PCOS. The original study was supported using the mean and
standard deviation of the glucose removal rate (GDR) to estimate the sample size required to
measure a GDR change of at least 20% from the baseline. With a prospective (paired) study design
with a target power of 80% and a significance level set to α=0.05, we can conclude that only 6
subjects are required to detect a 20% change in GDR from the start.
The main results of this study were previously reported in Moro et al. [103] and in Redman
et al. [106] The diagnosis of PCOS is assessed by Rotterdam criteria. [107, 108] Women with
PCOS must have the following two criteria: confirmation with medical history menstrual

61
irregulation (oligo or amenorrhea), the presence of more than 10 ovarian follicles 2-9mm in
diameter as assessed by MRI, or either clinical (hirsutism score) or serum excess androgen size
(increased free androgen index, FAI). Other causes of oligomenarche (hyperprolactinemia,
congenital adrenal hyperplasia, Cushing's syndrome, hyperthyroidism) are excluded by medical
history. Women in the control group were excluded from participation in our study for exercise
exercise, contraceptive drug use, and menstrual cycle irregularities along with excess
androgens. All women in our control group had an FAI value below 3.6 as defined as the cut-
off value for FAI in the PCOS assessment according to Hahn et al. [109] In addition, all women
in our control group reported regular periods, thus confirming that they did not have PCOS
based on Rotterdam guidelines. Potential subjects are excluded from participating in any of the
groups if they smoke, take any medications, have a history of current or past cardiovascular
disease, hypertension (>140/90 mmHg), diabetes (type 1 or type 2), kidney, liver or heart
disease, alcoholism or substance abuse, are pregnant or trying to conceive and are unable to
comply with an exercise training program.
The size of adipose tissue was reported in all participants included in this study. The size of fat
cells was determined using osmium fixation and calculated using a Coulter 3 multisizer counter
(Beckman Coulter, Brea, CA) as described earlier [110]. In vitro measurements of stroma-derived
adipocytes were reported from five women with PCOS before and after exercise due to the
availability of adipose tissue material for isolation and stroma-vascular cell culture. For
immunocytochemical analysis of lipid droplet and protein immunooblotting, controls were taken
from 5 women with normal menstrual cycles unrelated to the original study matched for age (24.2
± 2.3 years, p = 0.37 compared to women with PCOS) and

62
BMI (26.1 ± 2.5 kg/m2, p = 0.83 compared to women with PCOS)—this is necessary because the
collection of stroma-derived adipose cultures was not part of the initial study protocol for control
subjects. The design and protocol of the study were approved by the institutional review board of
the Pennington Biomedical Research Center, and all volunteers gave written approval. This study
was registered in clinicaltrials.gov (NCT01150539).
All women were examined at the beginning, and women with PCOS were re-examined
after 16 weeks of aerobic exercise training. At each time point, the testing of the study took place
over 3 days. To reduce the confounding factors associated with differences in diet and metabolic
testing, we gave participants a standard diet of 50% carbohydrates, 35% fat, and 15% protein 2
days before testing and during the duration of the test. After overnight fasting, blood abdominal
and subcutaneous adipose tissue samples were collected, body composition (the presumed
percentage of body fat from all body parts) was assessed by dual-energy x-ray absorptiometry
(DXA, QDR 4500A; Hologics, Bedford, MA), and insulin sensitivity are determined by
hyperinsulinemic-euglycemic clamps (120 minutes at 80 mU/min/m2) as described earlier [106].
Aerobic capacity (VO2max) was measured during a multi-level treadmill test (TrueMax 2400;
ParvoMedics, Salt Lake City, UT). Serum testosterone and sex hormone-binding globulin were
determined by automated chemiluminescent immunoassay at Immulite 2000 (Siemens Healthcare
Diagnostics, Deerfield, IL). Serum glucose and serum insulin were measured by enzymatic assay
on the Beckman Coulter DXC 600 (Beckman Coulter, Brea, CA). The morphology of the ovaries,
abdominal subcutaneous adipose tissue (SAT), and visceral adipose tissue (VAT) as well as
intrahepatic lipids and intramyocellular lipids (IMCL) of soleus are

63
examined before and after 16 weeks of aerobic exercise exercise using 3T MRI/MRS (GE 3.0T
Signa EXCITE MRI, GE Healthcare, Pittsburgh, PA; results are provided in Table 1).
4.2.2 Magnetic Resonance Imaging and Spectroscopy
Abdominal fat: An 8-channel torso arrangement coil is placed over the chest/abdominal
area and a 3.4 mm slice (1.7 mm junction gap) is obtained from the highest point of the liver to
the inferior pole of the right kidney. A total of around 220 images were obtained for each
participant. Total abdominal adipose tissue mass (TAT), visceral (VAT) and subcutaneous
(SAT) were calculated using the Analyze TM software package (CNSoftware, Rochester, MN).
Muscle and liver lipid content: For intramyocellular lipid measurement of muscles, the right leg is
positioned inside the 1H knee coil with the knee in the extension and the ankle in the neutral position. Separate water-pressed
PRESS boxes (voxel 10 x 7.5 x 7.5 mm) were collected from the anterior tibialis (n=1), soleus
(n=3) and peanut oil phantom (n=1). For liver lipid content, with participants lying on their
stomachs, a 1H body coil was placed over the torso and one PRESS box (30 x 30 x 30 mm) was collected in an area of the liver free from
severe vascularization. The data was analyzed using the jMRUi software package. Ovarian morphology:
An 8-channel torso arrangement coil is used to obtain the coronal (T2-weighted fast-turn Echo
(FSE), short T1 inversion recovery (STIR), and T1-weighted localization), sagittal (T1-weighted
localization only) and axial (T2-weighted FSE and STIR). Images were obtained from the highest
point of the uterus or ovary through the bottom of the ovary with a 4mm thick slice and a 1mm
intersection gap for a total of about 40 images. Images were analyzed using Analyze™ 8.1
(CNSoftware, Rochester, MN) by trained analysts. The ovaries, as well as the ovarian follicles, are
found and measured on each coronary FSE image. The follicle is located in the image and is
followed

64
through the remaining successive images to ensure that each individual follicle is identified as
such. The total number of follicles in each ovary is calculated using this technique. The volume
of each follicle is calculated based on the number of pixels measured in each image and the
number of consecutive images in which the follicle is located.
4.2.3 Subcutaneous Adipose Tissue Biopsy
Subcutaneous adipose tissue was obtained from the upper left quadrant of the abdomen
with a 5 mm Bergstrom needle using the Bergstrom technique. The skin is cleaned with a
povidone-iodine solution, a sterile curtain is placed over the incision site, and local anesthesia (a
5 mL 1:1 mixture of 0.5% bupivicaine and 2% lidocaine) is administered. An incision of about
1cm is made and adipose tissue is collected.
4.2.4 Sports training program
Aerobic exercise is done under supervision at Pennington Health and Fitness Center, five
times per week. Aerobic exercise is prescribed individually with the aim of achieving a specific
exercise energy expenditure (ExEE) in each session. During the first four weeks, the ExEE target
was 4% of the participants' estimated energy needs for weight maintenance, and increased to 6%
for weeks 5-8, to 8% for weeks 9-12 and to 10% for weeks 13-16. All exercises are performed on
the treadmill at 55% VO2max, moderate intensity. The velocity and gradient required to achieve
ExEE are estimated from the linear regression of absorption and O2 workload during the VO2max test
and ExEE is confirmed once during every 4-week interval by indirect calorimetry. Heart rate is
monitored during all sessions to verify ExEE. The training time required to complete the energy
expenditure target is 23±1 minutes per session during weeks 1-4, 35±1 minutes per session during
weeks 5-8,

65
47±2 minutes per session during weeks 9-12 and 58±2 minutes per session during weeks 13-16.
To prevent variation in outcomes due to dietary influences during the seniority intervention, we
asked participants to maintain their dietary habits throughout the 16 weeks of the intervention as
they would before study enrollment. In addition, we ask for updates on food intake during site
visits for training sessions.
4.2.5 Stroma-derived adipocyte cultures, immunofluorencenc staining, lipolysis, triglyceride
determination, and oleic oxidation
Samples of adipose tissue from the subcutaneous abdominal depot were collected under
aseptic conditions and isolated stromovascular (SV) cells were cultured as described earlier
[111] and differentiated as previously described [112] by modifications: DMEM-F12 medium
(1:1) plus 10 mg/ml transferin, 33 μM biotin, 17 μM calcium pantothenate, 0.5 μM insulin,
0.1 μM dexamethasone, 0.2 nM triiodothyronin, as well as 0.5 μM Roziglitazone, and 540 μM
IBMX during the last 48 hours of culture. All experiments were performed on cells after 9 days
of differentiation. Cultures were stained for lipids (BODIPY, 10 μg/ml) and DNA (DAPI, 300
nM) (Invitrogen, Carlsbad, CA). The image was obtained using a Leica TCS SP5 AOBS resonance
scanning confocal microscope (Leica AG, Wetzlar, Germany). The lipolysis test was carried out
for 3 hours by adding 0.2 ml of HBSS + 2% BSA. At the end of incubation, the media was
collected for glycerol measurements, performed in duplicate using free glycerol reagents (Sigma-
Aldrich, St. Louis, MO) and adjusted to the triglyceride content. Triglyceride levels were then
measured using the glycerol phosphate oxidase triglyceride determination kit (Sigma-Aldrich, St.
Louis, MO) and normalized by protein content. Cultures are pre-incubated for 3 h with [ 1-14C] oleic
acid (1 μCi/ml; PerkinElmer, Boston, MA) and non-label oleic acid (cold) (100 μM).

66
Oleic acid is combined with fatty acid-free BSA in a molar ratio of 5:1. After incubation, 14CO2
was measured as described earlier [113] The cells were then lysed in 0.2 ml of 0.1% SDS for the
determination of cell-related label uptake and protein content for normalization. All tests are
carried out in duplicate.
4.2.6 Real-time qRT-PCR and Western Blotting
Total RNA was extracted from approximately 100 mg of adipose tissue using the
miRNEasy kit (Qiagen, Valencia, CA) according to the manufacturer's specifications. RNA
extracts were converted into cDNA using a High Capacity cDNA Reverse Transcription Kit
(Applied Biosystems, Foster City, CA) and stored at -20°C until Real Time-PCR was performed.
Gene expression was carried out using Real Time-PCR with TaqMan-on-demand gene expression
test on the ABI 7900HT Fast Real-Time PCR System (Applied Biosystems, Foster City, CA).
Gene expression tests were performed for the following genes: PLIN1 (Hs00160173_m1), PLIN2
(Hs00765634_m1), PLIN3 (Hs00998421_m1), PLIN4 (Hs00287411_m1), PLIN5
(Hs00965990_m1), GBF1 (Hs00188327_m1), ARF1 (Hs00796826_s1), ARFRP1
(Hs00182389_m1), βCOP (Hs00200674_m1), Sec23a (Hs00197232_m1), ATGL
(Hs00386101_m1), CGI-58 (Hs01104373_m1), MGL (Hs00200752_m1), DGAT2
(Hs01045913_m1), mtGPAT (Hs00326039_m1), PPIA (Hs99999904_m1). Relative gene
expression was assessed using a standard curve of mRNA concentrations known and normalized
to Cyclophilin A gene expression (PPIA). Protein extracts from adipose cultures were
immunobloted and examined with antibodies against PLIN3 (Novus Biologicals, Littleton, CO)
and normalized against GAPDH loading control (AbCam, Cambridge, MA).

67
4.2.7 Statistical analysis
All analyses were performed using Prism GraphPad Software, version 5.0 (GraphPad
Software, La Jolla, CA). The Mann-Whitney test was used for cross-sectional comparisons
between PCOS and Obese Control women when the data were not normally distributed, and the
Independent Sample t-test was used when the data were normally distributed. Paired t-tests were
used to compare variables from the beginning to the end of the exercise training intervention;
except when the data is not distributed normally, the Wilcoxon Signed Ranked Paired test is used.
P < 0.05 is considered statistically significant. All graphical data is presented as SEM ± averages.
4.3 Result
4.3.1 Comparison of control vs. women with PCOS
Compared to control participants, women with PCOS had increased serum testosterone and
free androgen indexes, as expected, but they did not differ in terms of sex hormone-binding
globulin (SHGB) (Table 4.1). Otherwise, control participants were effectively matched with
women with PCOS for body composition, insulin sensitivity (fasting glucose, fasting insulin,
glucose elimination rate, HOMA-IR), and energy metabolism (resting metabolic rate, fasting
respiratory intelligence (RQ), metabolic flexibility (i.e. change between RQ and fasting RQ during
stable state of hyperinsulinemic euglycemic clamp) and VO2Max (Table 4.1).
Importantly, women with PCOS did not differ from control participants with respect to the average
subcutaneous fat cell size (Table 4.1).
68
Table 4.1: Anthropometric, metabolic, and serum markers for cross-sectional studies and
sports training interventions. These data reflect the 5 women with PCOS for whom we were
able to obtain adipose cultures derived from the primary stroma both before and after the exercise
intervention. follicles measured between 2-9mm in diameter could only be detected in 3 of the 8
control participants, but all women with PCOS had more than 10 follicles between 2-9mm in
diameter. EMBS: Estimated Average Body Size, FM: Fat Mass, FFM: Fat-Free Mass, GDR:
Glucose Excretion Rate, RQ: Respiratory Results, DHEA-S: Dehydroepiandrosterone Sulfate,
SHGB: Sex Hormone-Binding Globulin, FAI: Free Androgen Index, AT: Adipous Tissue, IHL:
Intrahepatic Lipids, IMCL: Intramyocellular
Women
with
PCOS
Contr
ol vs
PCOS
Before vs
After
Training
Control
Pre-
Workout
Post
Training
P value
P value
Age (yrs)
29.7 ± 12.4
27.0 ±2.9
--
0.65
--
Weight (kg)
78,9 ± 15,7
82.2 ± 18.2
81,4 ±21,6
0.74
0.69
BMI (kg/m2)
26.5 ± 5.4
30.8 ± 4.2
30.4 ± 5.8
0.17
0.66
Total body fat (%)
29.9 ± 9.8
36.8 ± 5.0
34.8 ± 6.1
0.19
0.21
FM (kg)
23.3 ±9.3
30.8 ± 11.1
29.3 ± 13
0.23
0.39
FFM (kg)
55.6 ± 15.9
51.4 ± 7.9
52.1 ± 9.0
0.60
0.24
AT visceral (kg)
1.4 ± 0.8
1.2 ± 0.5
1.1 ± 0.7
0.75
0.64
69
AT subkutan (kg)
11.4 ± 1.8
10.9 ± 4.8
10.5 ± 5.7
0.86
0.47
IHL (AU)
0,013 ±
0,017
0,13 ± 0,17
0,03 ± 0,05
0.16
0.20
IMCL (soleus, AU)
0,006 ±
0,003
0,006 ±
0,004
0,007 ±
0,005
0.89
0.27
Glukosa, puasa
(lime/dL)
103,5 ±
28,6
82.2 ± 6.3
89,6 ± 5,5
0.14
0.08
Insulin, puasa (mg/dL)
11.0 ± 10.2
9.8 ± 3.9
12.4 ± 5.6
0.81
0.51
HOMA-IR (AU)
3.4 ± 4.2
2.0 ± 0.8
2.7 ± 1.2
0.50
0.42
GDR/EMBS
(mg/kgFFM
+17.7)
6.8 ± 4.3
6.3 ± 1.2
7.6 ± 1.6
0.79
0.02
Metabolic Break
Rate/FFM (kcal/day/kg)
30.3 ± 4.8
30.7 ± 5.0
30.0 ± 2.7
0.91
0.62
RQ Break
0,80 ± 0,03
0,81 ± 0,02
0,80 ± 0,01
0.37
0.21
RQ Clamp
0,93 ± 0,07
0,90 ± 0,04
0,90 ± 0,05
0.50
0.83
ΔRQ (Clamp vs Break)
0,13 ± 0,07
0,09 ± 0,02
0,10 ± 0,03
0.26
0.72
VO2max (mL/min/kg)
27.7 ± 10.0
29.5 ± 3.0
33,6 ± 4,3
0.71
0.04
Fat Cell Size (nL)
0,69 ± 0,31
0,68 ± 0,13
0,76 ± 0,25
0.92
0.40
Testosteron (ng / dL)
35.4 ± 11.7
92.4 ± 41.2
64.8 ± 25.3
0.002
0.61
SHBG (nmol/L)
24.1 ± 4.6
30,9 ± 31,7
34.2 ± 19.3
0.56
0.75
70
DO (ME)
5.1 ± 1.4
18.8 ± 14.2
13.9 ± 17.5
0.02
0.67
Number of ovarian
cysts (diameter 2-
9mm)
a
29.4 ± 46.1
97 ± 29.7
119,4 ±
28,6
0.008
0.10
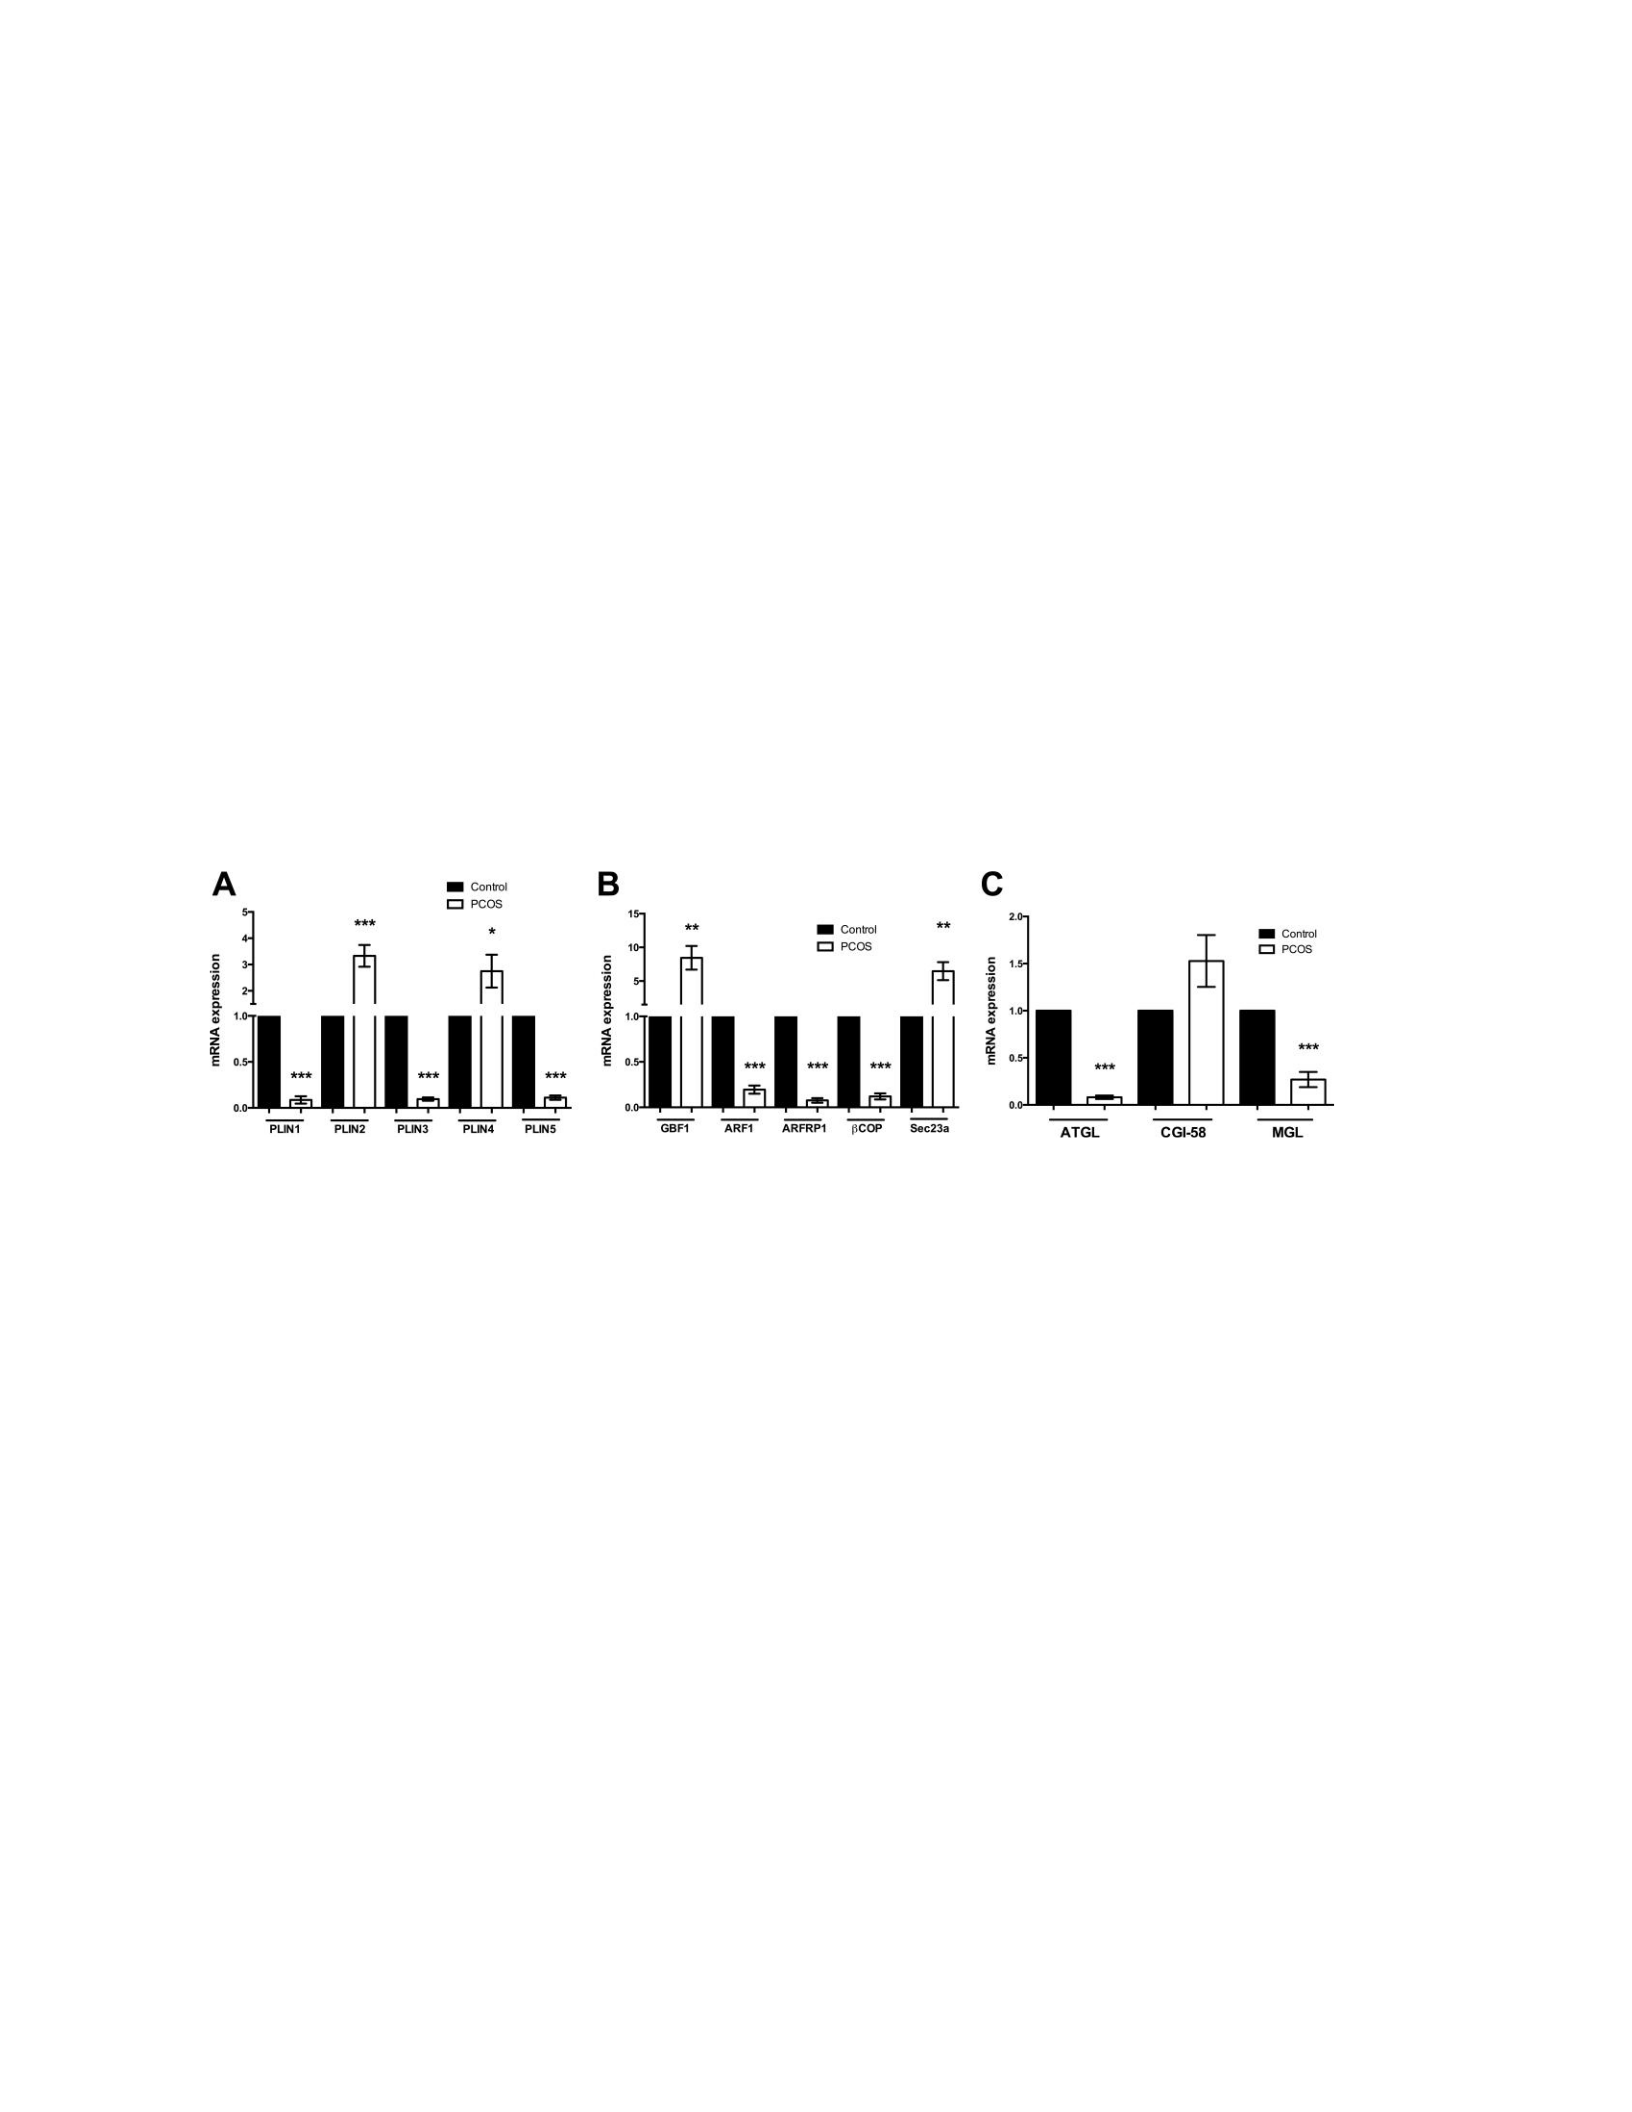
71
However, women with PCOS differed significantly from the controls in terms of gene expression
in subcutaneous adipose tissue for candidates responsible for lipolysis, lipid droplet perilipin
proteins, and coatomic proteins. As shown in Figure 4.1A, perilipin 1, 3, and 5 (PLIN1, PLIN3,
and PLIN5, respectively) were ~80-90% lower in women with PCOS when compared to controls,
while perilipin 2 (PLIN2) and perilipin 4 (PLIN4) were about 3 times higher. Expression levels of
coatomic mRNA GTPases ARF1, ARFRP1, and βCOP (Figure 4.1B) were ~80% lower in women
with PCOS compared to controls, with GBF1 and Sec23a expressed ~9 and 7 times higher,
respectively. Finally, the expression of mRNA lipase ATGL and monoglycerol lipase (MGL) was
reduced by 90% and 65%, respectively, with no difference in CGI-58 expression (Figure 4.1C).
Figure 4.1: Gene expression of abdominal subcutaneous adipose tissue from women with
PCOS versus age, BMI, and percentage of fat matched to control (cross-sectional study). A)
Perilipin family protein gene expression of all five perilipin proteins shows drastic differences in
expression. Perilipin 1 (PLIN1), perilipin 3 (PLIN3), and perilipin 5 (PLIN5) were all expressed
about 90% lower in women with PCOS compared to controls. Perilipin 2 (PLIN2) and perilipin 4
(PLIN4) were expressed about 3 times higher when compared to controls. B) The coatomeric
proteins involved in ER-to-Golgi transport are also regulated differently at gene expression levels.
ADP-ribosylation factor 1 (ARF1), ARF-associated protein 1 (ARFRP1), and beta-coatomer
(βCOP, part of the COPI complex) are drastically reduced in women with PCOS.

72
The resistance factor Brefeldin A exchange of GDP 1 (GBF1, which operates in conjunction with
ARF1) and Sec23a (part of the COPII complex) were both expressed about 8-fold higher in women
with PCOS. C) Adipose Triglyceride Lipase (ATGL) and Monoglyceride Lipase (MGL)
expression were both reduced in women with PCOS at gene expression levels, while there was no
statistically significant difference in the expression of the CGI-58 ATGL co-activator. *P < 0.05;
**P < 0.01; P < 0.001
4.3.2 Effect of Sixteen Weeks of Aerobic Exercise Exercise on Women with PCOS
Aerobic exercise resulted in a ~10% increase in maximum aerobic capacity (VO2Max,
p=0.04) and a ~20% increase in glucose scavenging rate (p=0.02) (Table 4.1). No other changes
were noted in terms of body composition, size of abdominal adipose depots (visceral or
subcutaneous depots), accumulation of ectopic lipids (in the liver or muscles), or fat cell size
(Table 4.1). However, changes were seen in gene expression in adipose tissue after exercise. Of
all the perilipins measured, only PLIN3 expression was significantly increased (p<0.05; Figure
4.2A), while PLIN1, PLIN2, PLIN4 and PLIN5 are unchanged. On average, the expression of
ARF1, ARFRP1, βCOP, and Sec23a increased by approximately 5, 8, 7, and 4-fold (p<0.05),
respectively, without any change in GBF1 (Figure 4.2B). In addition, the lipase of ATGL, MGL
and the co-activator ATGL CGI-58, increased significantly after sixteen weeks of exercise
(p<0.05; Figure 4.2C).
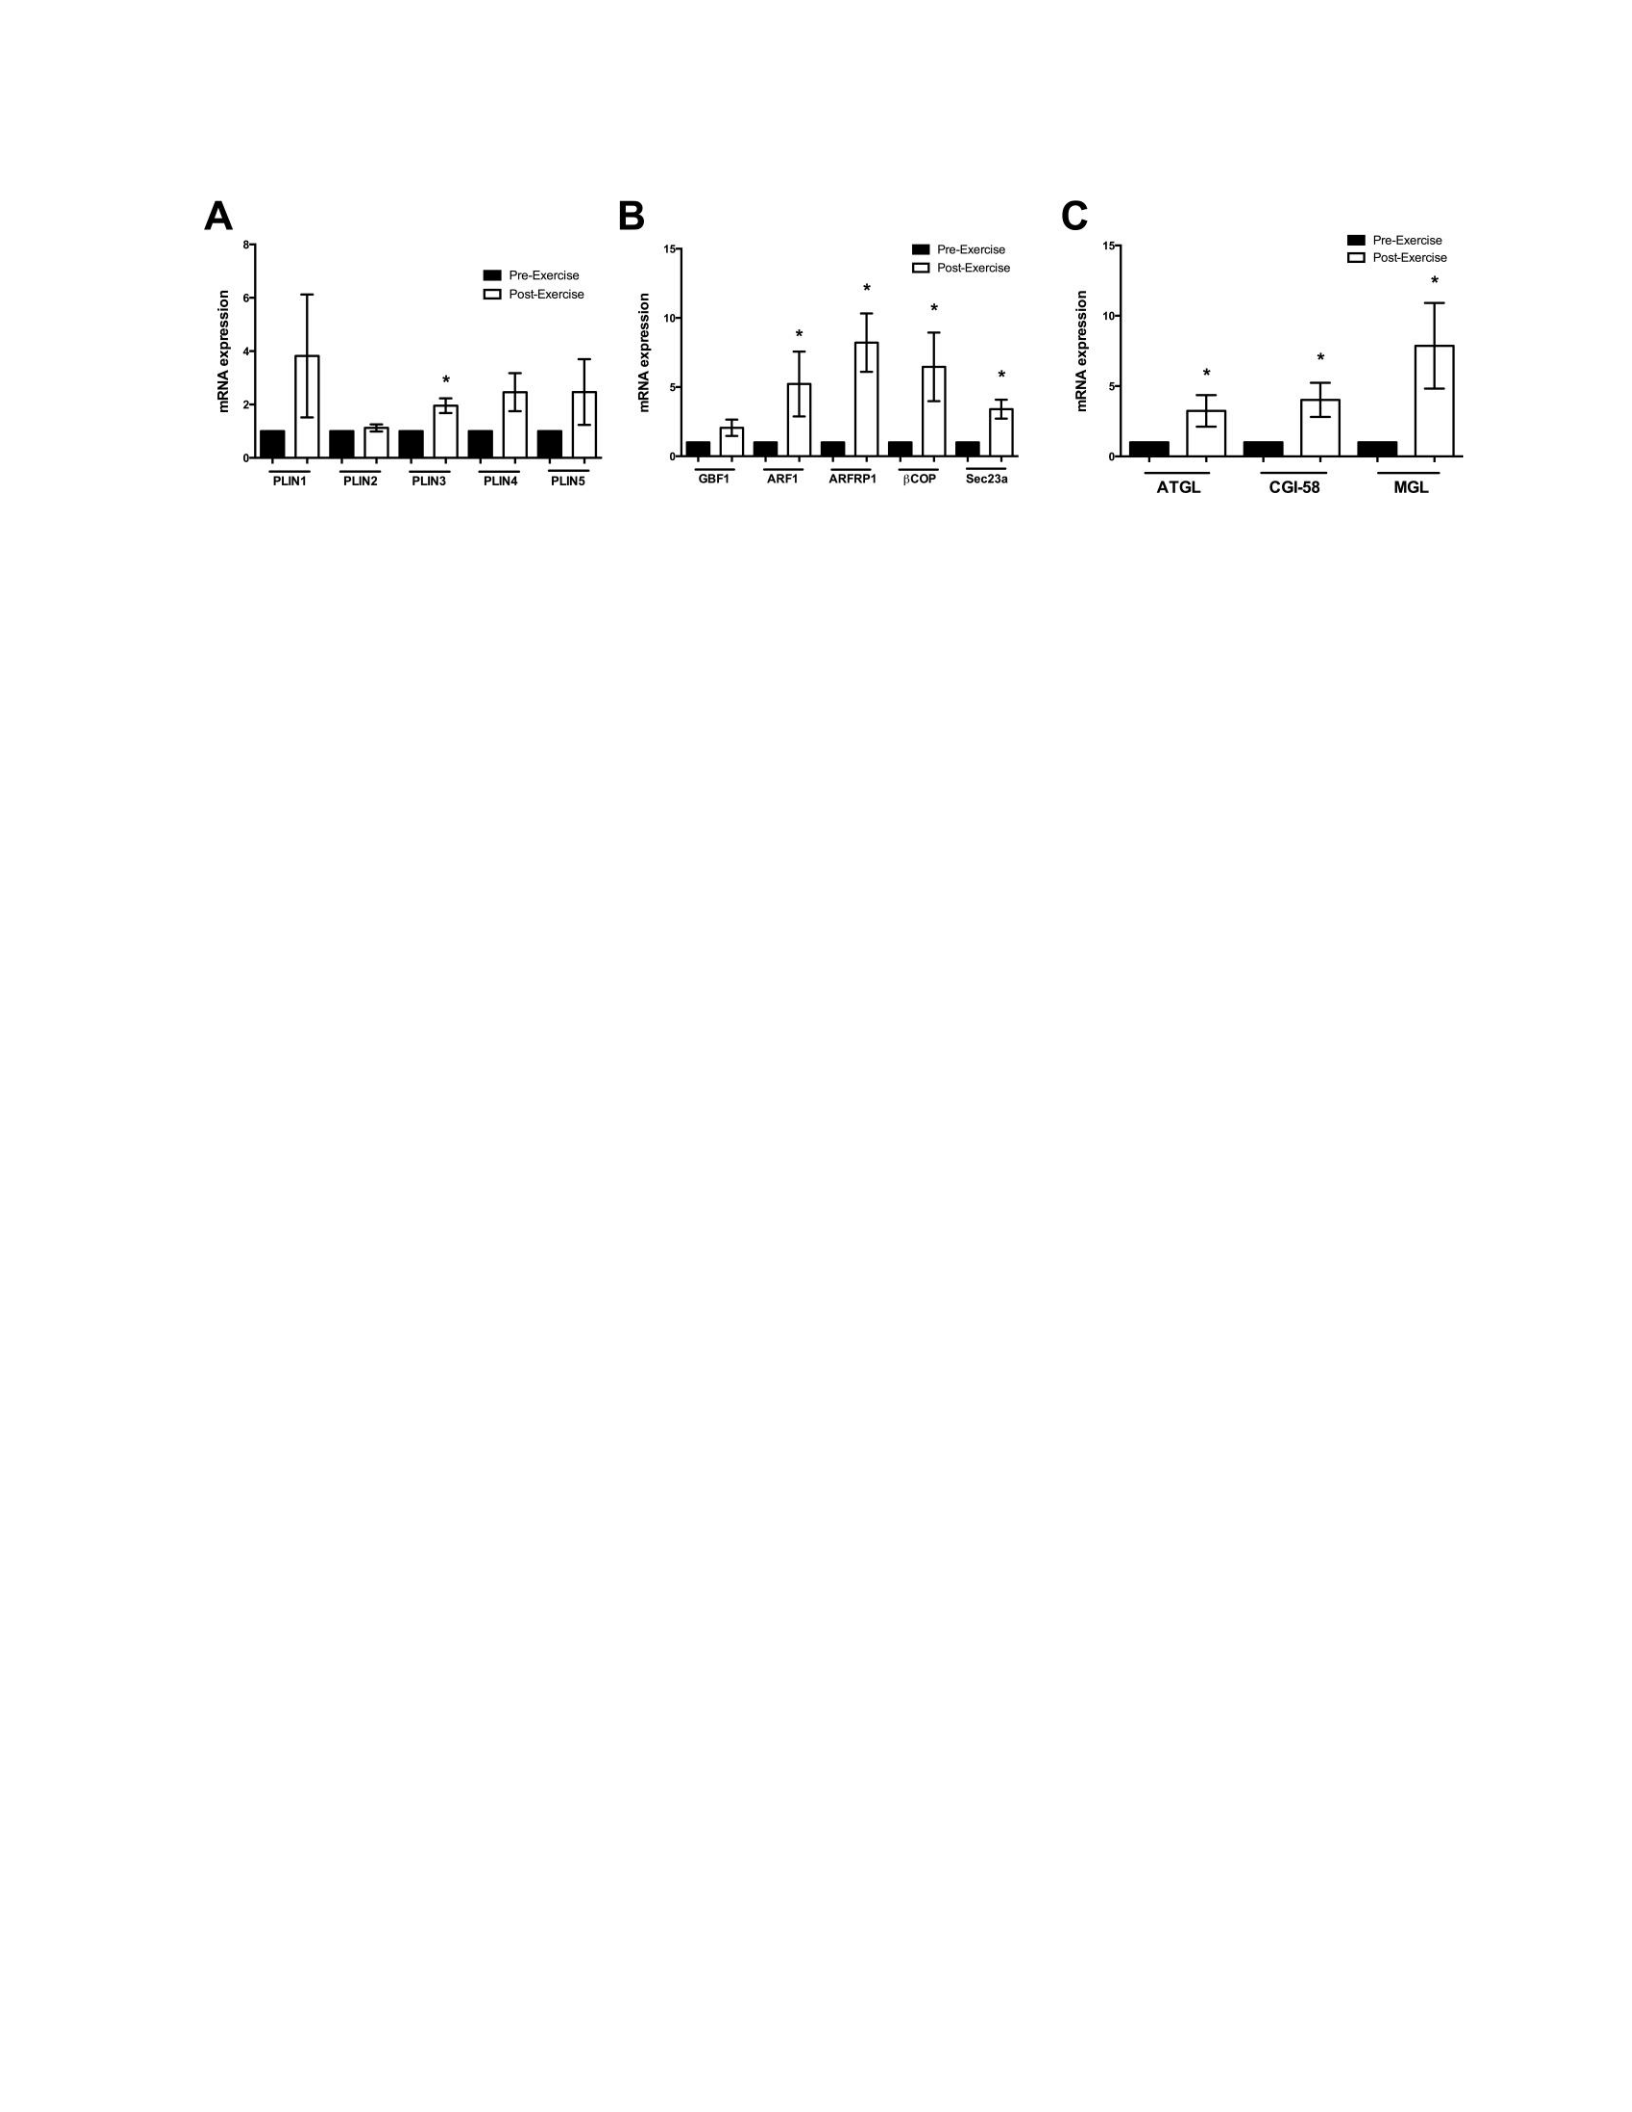
73
Figure 4.2: Gene expression targets in adipose tissue known to be involved in lipid droplet
regulation and lipolysis were altered at 16 weeks of exercise training in women with PCOS
(Sports training intervention, women with PCOS only). A) Gene expression of the perilipin
protein family from before to after exercise showed that only PLIN3 increased significantly after
exercise exercise. B) Expression of coatomeric genes reveals that ARF1, ARFRP1, βCOP, which
are greatly decreased when compared to control before exercise exercise, reveal an increase in
their expression. Sec23a is also improved after practice training. C) Expression of ATGL and MGL
genes, which are blunt when compared to control at the start, increase with exercise exercise. In
addition, CGI-58 increases after practice exercises. *P < 0.05
4.3.3 Lipid Droplet Morphology of Primary Adipose and Lipolytic Cultures
As shown in Figure 4.3, primary adipocyte cultures reveal a larger lipid droplet
morphology in women with PCOS compared to controls, which decrease in size after exercise
exercise, and thus are more similar to the morphology of control women (Figure 4.3). In vitro
measurements of fat oxidation and lipolysis on primary culture adipocytes showed that oleic
oxidation and glycerol release increased after exercise (p<0.05, Figures 4.4A and 4.4B). Similarly,
the total triglyceride content decreased after exercise (p<0.05, Figure 4.4C). Since PLIN3 is the
only perilipin that significantly increases adipose tissue at the mRNA level, we measured the level
of PLIN3 protein in primary adipose cultures. We discover virtually
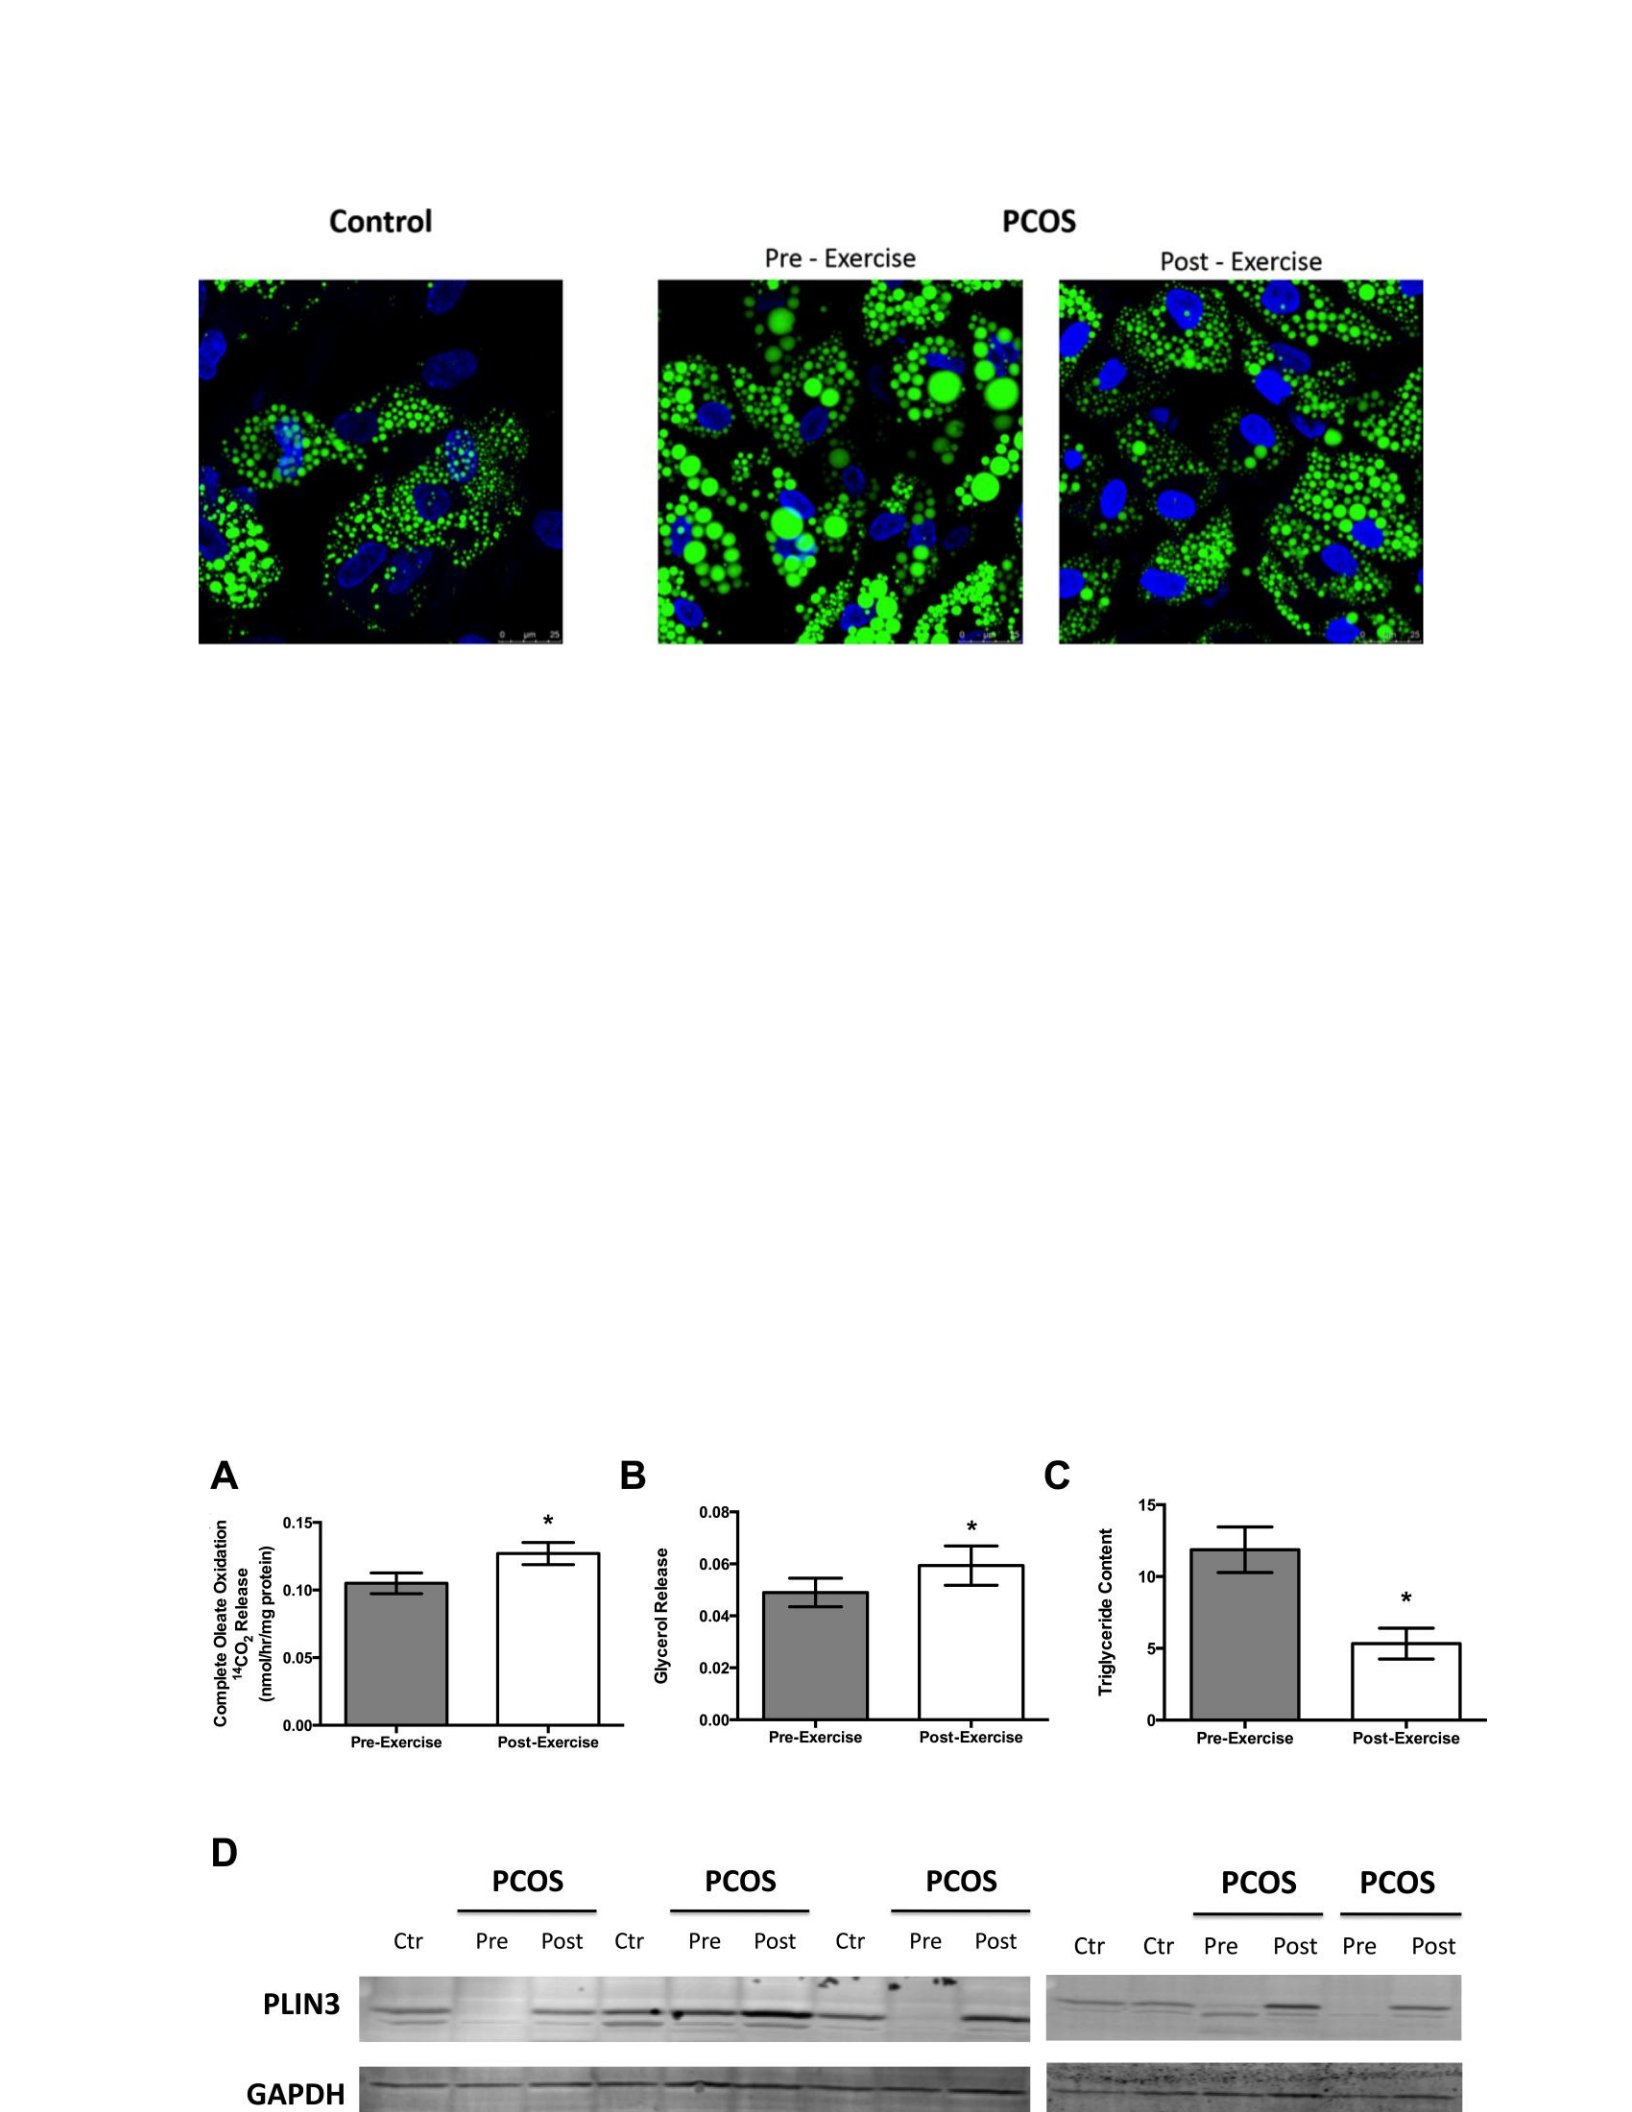
74
Figure 4.3: Representative image of stroma-derived adipocytes cultured and
differentiated into adipocytes. Women with PCOS had large lipid droplets when compared to
age-adjusted control donors, BMI, and % fat. The lipid droplet morphology appeared to
resemble the controls in our cross-sectional study after 16 weeks of aerobic exercise training in
women with PCOS. Bodipy 494 (Green) is used to identify lipids and DAPI (Blue) is used to
identify the nucleus.
levels of PLIN3 were absent in 4 out of 5 women with PCOS, while PLIN3 expression was present
in controls (Figure 4.4D). Exercise induced PLIN3 protein expression in 4 women with PCOS,
who had no PLIN3 protein expression before exercise, and increased compared to pre-workout
expression in one woman with PCOS, who had PLIN3 protein expression before exercise (Figure
4.4D).

75
Figure 4.4: Oxidation study of ex vivo oleate in stroma-derived adipose cultures from women
with PCOS and PLIN3 protein content. An ex vivo oleic oxidation study revealed that stroma-
derived adipose cultures from women with PCOS had increased oleic oxidation measured by 14C
labeled CO2 (A) after 16 weeks of exercise exercise. Furthermore, glycerol release into the culture
medium was increased (B) and total triglyceride content was reduced (C) in adipose cultures of
women with PCOS after exercise exercise. D) Cross-sectional and exercise intervention
expression PLIN3, the only perilipin protein that increases adipose tissue in women with PCOS
after exercise training at the gene expression level, was found to be almost absent in 4 out of 5
women with PCOS donors when compared to controls in their primary adipocyte cultures.
Likewise, expression levels increased in all 5 women with PCOS after exercise exercise in their
primary adipose culture. *P < 0.05
4.4 Discussion
Our data highlight a previously unrecognized potential role of perilipin 3 in adipose tissue
lipolysis in women with PCOS. We showed for the first time that PLIN3 expression, along with
PLIN1 and PLIN5, was greatly reduced in adipose tissue in women with PCOS when compared
to age and body composition – and metabolically fit women. PLIN3 mRNA expression
increased—the only significantly increased perilipin protein—after 16 weeks of aerobic exercise
training in women with PCOS. In addition, stroma-derived primary adipose cultures from PCOS
women revealed that almost no PLIN3 protein was expressed before exercise exercise, but was
expressed after exercise coupled with increased oleic oxidation. We previously reported that
exercise training in this cohort increased adipose tissue lipolysis under adrenergic stimulation

76
[103]. Our data suggest that PLIN3 may partially contribute to increased stimulation of adipose
network lipolysis.
The benefits of exercise associated with improved PCOS symptomatology have been
thoroughly investigated. Studies have shown for women with PCOS an increase in insulin
resistance [98, 99, 114, 115], serum lipids [114, 116], and risk of cardiovascular disease [98, 99,
114, 117]. In addition, improvement in menstrual cycles has been shown after exercise intervention
in women with PCOS [98, 114, 118]. Although some studies have shown weight loss with
exercise[98, 99, 114], some studies have shown that benefits occur without weight loss[106, 115,
119] and suggest that exercise for PCOS would be recommended even if weight loss is not
achieved. Our study showed an increase in insulin resistance measured by euglycemic clamps-
hyperinsulinemic clamps (Table 4.1) and an improvement in menstrual function [106]. However,
despite all these benefits of exercise, several studies have investigated molecular targets in adipose
tissue from women with PCOS. This appears to be important given the reported defects in adipose
tissue function previously shown in women with PCOS (reviewed in [86]). We previously reported
that 16 weeks of aerobic exercise may increase basal and catacholemine stimulation lipolysis in
adipose tissue [103]. Previous investigations have shown one nucleotide polymorphism was found
in women with PCOS for the perilipin gene[104], suggesting a potential defect in the perilipin
protein family, which is involved in lipolysis. Here, we have investigated the targets that regulate
adipose tissue lipolysis, with an emphasis on PLIN3 given the increased regulation of gene
expression seen in adipose tissue with exercise.
Studies centered on the perilipin protein family have focused heavily on the involvement
of PLIN1 in the regulation of lipolysis in adipose tissue (reviewed in [120]) through PLIN1
phosphorylation coupling and ATGL activation [121, 122]. However, the possible role of PLIN3
regulation in adipose lipolysis is largely ignored. Studies have shown PLIN3 is highly expressed

77
in adipocytes and is described to have a preference for PLIN3 to coat smaller lipid droplets [123].
In addition, studies in HeLa cells have revealed the colocalization of ATGL to PLIN3-coated lipid
droplets during lipopolitical stimulus [44, 47].
In addition, several studies investigating the role of PLIN3 in skeletal muscle lipolysis suggest
that PLIN3 colocalizes to lipid droplets in mice during epinephrine and muscle contractile
stimulation [43, 45]. Research from our group recently showed that PLIN3 expression was
regulated after aerobic exercise in skeletal muscle, regulated in response to lipolysis stimulation
in human primary skeletal myotube cultures, and was positively associated with ex vivo skeletal
muscle and in vivo whole-body fat oxidation [105]. Our data here, using in vivo and in vitro
systems, show that the link between PLIN3 and lipolysis is evident in female adipose tissue with
PCOS, suggesting PLIN3 as a potential novel mediator of lipolysis.
Our data also highlight previously uninvestigated coatomic GTPases that have the
potential to be involved in mediating lipolysis. We show lower expression of ARF1, ARFRP1,
and βCOP1 in women with PCOS compared to control; The expression of this target increased
rapidly after 16 weeks of aerobic exercise exercise in women with PCOS. Soni et al. showed
that ATGL is delivered to PLIN3-coated lipid droplets: a phenomenon that is inhibited when
treated with brefeldin A, a compound known to inhibit ARF1, or when multiple coatomic
GTPases, such as ARF1, Sec23a, βCOP, and GBF1 are knocked down [47]. Studies from our
group have shown that ARF1, Sec23a, and ARFRP1 improve their expression with aerobic
exercise in skeletal muscle and by lipolytic stimulation in primary skeletal muscle cultures
[105]. Finally, Guo et al. discovered the differential expression of coatomic GTPase with respect
to the morphological differences of lipid droplets [22]. Likewise, we showed that despite the
difference in fat cell size, women with PCOS had a larger lipid droplet morphology when
compared to their age and body composition matched the controls. The morphology of lipid

78
droplets was more similar to that of control women after 16 weeks of aerobic exercise in women
with PCOS. These alterations to the coatomic GTPase may be involved in regulating lipolysis
not only as a mediator of lipase delivery to lipid droplets, but also as a regulator of lipid droplet
morphology. Further functional investigations are needed to determine this mechanism.
We also observed reduced expression of mRNA lipase (both ATGL and MGL) in adipose
tissue of women with PCOS, compared to controls. Lipase expression increases with exercise,
which is expected given the increase in lipolysis in vivo and in vitro. One aspect of lipase
expression that is still elusive is that previous investigations have shown that testosterone
mediates lipase expression [96, 97]. Our data show that lipase expression increases after exercise
without decreased circulation Total testosterone concentrations, or free androgen indexes, may
indicate that aerobic exercise may increase adipose tissue lipolysis despite altering testosterone
expression.
Furthermore, we speculate that the increase in lipase expression we observed is not fully
responsible for the increase in lipolysis after exercise exercise. In fact, previous reports have
shown that lipase does not act on its own on lipid droplets to facilitate lipolysis, but requires a
companion such as the perilipin protein (reviewed in [120]) or certain coatomic GTPases [47].
We realized that our results and conclusions were based on observational data and the
association between increased lipolysis, and expression of PLIN3 and coatomic GTPase after
exercise, and did not establish causal results. However, given the dominance of our findings and
data presented in previous investigations from our group and others, we believe that this
association is new and relevant to highlight potentially novel and unrecognized targets that may
partially mediate adipose network lipolysis. In addition, it was noted that we only performed sports
interventions in women with PCOS, as our original design was a prospective sports intervention
study for women with PCOS. Although we did not perform any exercise intervention in our control

79
group because cross-sectional components were added later, the aim of the study involving the
control group was to perform the same set of advanced assessments (clamps, MRI, fat cell size,
DXA) and to obtain a matched control group based on metabolic phenotype. Cross-sectional
comparisons showed a novel and strong difference between women with PCOS and controls and
were able to further demonstrate that exercise in women with PCOS can save lipolysis defects to
the levels observed in control subjects. Due to the rigorous design of our study, closely supervised
and monitored sports interventions, and extensive phenotypic analysis of women with PCOS
Before and after their exercise intervention, we are confident that we are sufficiently capable of
identifying upregulation of PLIN3 gene expression as well as coatomic GTPase, thus
demonstrating their potential role in increasing adipose tissue lipolysis after sports training. Further
investigation is needed to understand the specific mechanistic role of PLIN3 in adipose tissue
lipolysis.
In conclusion, based on previous evidence of single nucleotide polymorphism in the
perilipin gene [104], we investigated the expression of the perilipin protein family in adipose
tissue from women with PCOS, and have shown that some perilipin proteins are expressed
differently in women with PCOS compared to the age and body composition matched to that of
the control women. We have also shown that coatomeric GTPases (ARF1, Sec23a, βCOP, GBF1,
ARFRP1) are expressed differently in women with PCOS. Sixteen weeks of aerobic exercise
significantly improved the expression of PLIN3 as well as coatomic GTPase (ARF1, Sec23a,
βCOP, GBF1, ARFRP1). Primary adipose cultures derived from the stroma showed increased
lipolysis in vitro, oleic oxidation, and reduction in triglyceride content after exercise exercise. In
addition, adipose cultures expressed almost no expression of PLIN3 protein before exercise,
which was then enhanced/expressed after exercise exercise. Finally, primary adipose cultures
showed the morphology of large lipid droplets, which were altered by exercise exercise, despite

80
the fact that there was no difference in the size of fat cells from adipose tissue cross-sectionally.
These data highlight previously unrecognized and novel potential targets that may be responsible
for increasing exercise-mediated lipolysis in adipose tissue of women with PCOS.
CHAPTER 5: GENERAL DISCUSSION

81
The overarching themes of this investigation highlight the previously unrecognized
potential of perilipin 3 (PLIN3) as a lipid oxidation facilitator in sedentary, but otherwise healthy
individuals, individuals with type 2 diabetes (T2D), and women with polycystic ovary syndrome
(PCOS). In addition, the coatomic protein gtp-ase, which had been investigated in a stable cell line
before, is now being measured for the first time in relation to lipopolitical stimulation in human
skeletal muscle and adipose tissue. As previously discussed, the current focus of research in this
area is heavily on other perilipin proteins, namely perilipin 1 (PLIN1) in adipose tissue as well as
perilipin 2 (PLIN2) and perilipin 5 (PLIN5) in skeletal muscle. Thus until now, the potential of
PLIN3 to serve as a target to induce lipid oxidation in individuals with T2D has been ignored.
However, the research provided here should serve as a catalyst for future investigations into the
therapeutic opportunities that PLIN3 and coatomic gtp-ase may offer to improve lipid metabolism
in skeletal muscle individuals with T2D.
The data presented in chapter 2, originally published in PLoS ONE in 2014, showed that
in primary skeletal muscle myotubes donated from sedentary, healthy men, epinephrine treatment
as well as treatment with a pharmacological cocktail of palmitate, forskoline, and ionomycin
(PFI), both of which were known to increase lipolysis, increasing the expression of PLIN3 protein
content. Coatomer gtp-ases, ARF1, ARFR1, and GBF1, increased protein content, and ARF1,
Sec23a, and GBF1, increased in mRNA expression after PFI treatment. This data was combined
with a clinical trial involving 20 healthy male participants, who underwent a single resistance
exercise that consumed 650kcal of energy with biopsies taken before and immediately after
exercise. Clinical results show improvement in PLIN3 skeleton

82
muscle protein content after exercise as well as a significant increase in mRNA levels of ARF1,
GBF1, and Sec23a. Changes in PLIN3 expression were significantly correlated, positively
correlated with changes in lipid oxidation in vivo throughout the body and skeletal muscle-
specific ex vivo palmitate oxidation. The combined results of this study showed that PLIN3 levels
increased with lipopolitical stimulation, whether pharmacological or physiological, in human
skeletal muscle at both in vitro and in vivo levels.
In chapter 3, utilizing a second clinical trial involving 29 sedentary men, originally
published in the Journal of Clinical Endocrinology and Metabolism in 2015, it was found that in
resting conditions, levels of skeletal muscle protein PLIN3 correlated with increased lipid
oxidation at the whole-body level both in vivo from 24-hour respiratory intelligence and in vivo
Specific palmitate oxidation of skeletal muscle tissue. This evidence independently reproduces the
data shown in chapter 2. Utilizing primary skeletal muscle myotube cultures, PLIN3 was
artificially knocked down using siRNA, and the lipid oxidation rate was drastically reduced. The
combination of these data from chapters 2 and 3 shows evidence that human skeletal muscle
PLIN3 is involved in reproducible lipid oxidation from two separate independent clinical trials, at
the specific level of whole body and tissue, and that PLIN3-induced knockdown by siRNA in
primary muscle culture reduces lipid oxidation in vitro.
The remainder of chapter 3 highlights the possibility that PLIN3-mediated lipid oxidation
function is a phenomenon seen only in primary muscle cultures taken from sedentary healthy
donors and donors with T2D. PFI treatment is used on myotube cultures from physically active
donors, sedentary but healthy donors,

83
and donors with T2D. Over the course of time after 3 days of PFI treatment, levels of PLIN3
protein as well as levels of coatomic protein gtp-ase ARFRP1 increased in myotubes from healthy
and sedentary donors and donors with T2D. However, myotubes from active donors did not
express much PLIN3 or ARFRP1, but rather expressed increased levels of PLIN5 protein.
Furthermore, by utilizing the pharmacological brefeldin A, a drug that inhibits the action of ARF1,
the level of lipid oxidation in vitro decreased significantly in the myotube of sedentary individuals
and individuals with T2D. However, brefeldin A had no significant impact on the oxidation rate
of myotube lipids from physically active donors.
These results reveal the potential of two separate metabolic pathways for lipid droplet lipid
oxidation mediated either by PLIN3 and coatomic gtp-ase or by PLIN5. With the evidence
presented, it appears at this point that individuals with T2D are more dependent on the PLIN3-
mediated pathway, which would suggest that further investigation into PLIN3 may uncover
potential therapeutic agents to increase skeletal muscle lipid oxidation in T2D.
Two questions remain after the investigation in chapters 2 and 3. First, although it was
shown that when PLIN3 was artificially knocked down in primary skeletal muscle cultures using
siRNA, the lipid oxidation rate decreased, did such knockdown exist in nature and what effect did
it have on lipid oxidation? Furthermore, all investigations so far have looked at the expression of
skeletal muscle PLIN3 and coatomic gtp-ases; But what about human adipose tissue? To answer
these questions, it is indicated in chapter 4, originally published in the European Journal of
Endocrinology in 2015, that women with polycystic ovary syndrome, a disease characterized by
infertility, hyperandrogenism, and insulin

84
resistance, naturally having levels of PLIN3 protein that is absent in their subcutaneous adipose.
Likewise, the mRNA levels of other major coatmer gtp-ases differed significantly when
compared to age- and weight-appropriate control women without PCOS, as well as wide variation
in lipid droplet morphology in primary adipose cultures. The women with PCOS underwent a 16-
week aerobic exercise trial, with repeated subcutaneous adipose biopsies and whole-body lipid
oxidation measured. After exercise exercise, the expression of PLIN3 protein is clearly visible in
adipose tissue, and the oxidation of lipids throughout the body increases. In addition, the
expression levels of coatomic mRNA gtp-ases ARF1, ARFRP1, COP1, and Sec23a were also
significantly increased, and the morphology of lipid droplets in primary adipose cultures
resembled control women
from the beginning of the trial. These data suggest that PLIN3-mediated lipid oxidation has the
potential to occur in adipose tissue after aerobic exercise and that naturally occurring PLIN3
knockdown is associated with decreased lipid oxidation levels.
Further research will be needed to understand the changes and mechanisms between the
PLIN3-mediated lipid oxidation pathway seen in sedentary individuals and the T2D and PLIN5-
mediated lipid oxidation pathway seen in active individuals.
Importantly, the results presented here are only shown at the in vitro level in primary muscle
culture. Regardless of how robust the primary tissue culture model is, it is important to see if these
same results can be translated to skeletal muscle tissue in vivo in individuals with T2D. In addition,
further research into adipose tissue of women with PCOS regarding PLIN3-mediated lipid
oxidation may also help improve metabolic outcomes from this insulin-resistant disease.

85
Further research can also be expanded to identify transcription factors that will regulate
increased expression of PLIN3, and pharmacological agonist testing of those transcription factors.
As explained in the introductory chapter, the transcription factors that control PLIN3 have not
been described. However, if pharmacological can be targeted to improve its expression, more
clinical investigations can be used to provide therapeutic benefits for patients with T2D.

