


1
CHAPTER I
INTRODUCTION
Due to the prevalence of disability in the United States, coupled with the high incidence
of economic, employment, and educational hardship experienced by people with disabilities,
rehabilitation counselor trainees have an increased responsibility to become competent social
change agents (Ratts & Hutchins, 2009). Social justice advocacy is defined as activism for social
change, particularly with a focus on oppressive social structures and systems (Marbley, Bonner,
Robinson, Stevens, Li, Phelan, & Huang, 2015); therefore someone who engages in social justice
advocacy is referred to as a social change agent. Social justice advocacy is a fundamental
competency in the rehabilitation counseling profession (Leahy, Fong, & Saunders, 2003; Leahy,
Muenzen, Saunders, & Strauser, 2009); however, little is known whether pre- service counselors
are prepared to engage in social justice advocacy (Waldmann & Blackwell, 2010).
Social justice in counseling is an approach used to promote equity, access, participation,
and harmony by challenging social barriers and other inequalities (Crethar & Ratts, n.d.). Social
justice advocacy is imperative in counseling; therefore, competencies and professional practices
have been adopted to ensure counselors are equipped to engage in advocacy. For instance, to
help conceptualize advocacy, a framework of interventions and strategies that occur on multiple
levels were created to guide counselors in social justice advocacy. These competencies are

2
endorsed in professional counseling by the American Counseling Association (ACA) (Lewis,
2011). Also, professional counseling standards and responsibilities have been established to
engage rehabilitation counselors in social justice advocacy and to execute competent
rehabilitation counseling services. According to the Commission on Rehabilitation Counselor
Certification (CRCC, 2017), the standards of ethical practice in the Code of Professional Ethics
(Section C.1.) indicate that rehabilitation counselors are competent in group, institutional,
individual and social advocacy. The Code further expresses the importance of competency in
advocacy practices and skills to include empowerment, organizational advocacy, advocacy and
consent, advocacy and confidentiality, and systems. Additionally, to ensure competent
rehabilitation services, the Code lists six critical principles that guide the work of rehabilitation
counselors:
Autonomy: To respect client rights and facilitate self-determination
Beneficence: To demonstrate support and advance the well-being of others.
Fidelity: To be reliable and trustworthy.
Justice: Give fair treatment and care to all.
Nonmaleficence: To do no harm onto others.
Veracity: To demonstrate truthfulness.
Social justice advocacy competency has become steadily pertinent in rehabilitation
counseling due to the growing representation and prevalence of disability in the U.S. population
and counselors have an increased responsibility for providing competent rehabilitation services
to these populations. Disability populations indicate millions of persons living with a disability
with many receiving services and treatment from a counseling professional. According to a U.S.
Disability Statistics report in 2016 reflecting all disability types, genders, ages, races, and

3
educational levels, an estimated 12.8 percent or 40,890,900 million, non-institutionalized persons
disclosed a disability. Major depression is expected to be the second most common cause of
disabilities by 2020 (WHO, 2016) and according to The National Institute of Mental Health,
about 44.7 million adults aged 18 or older were identified to have a mental illness of which an
estimated 19.2 million received mental health treatment within that past year. Furthermore, an
online survey of more than 2,100 U.S. adults was conducted by Harris Interactive on behalf of
University of Phoenix in March 2013, which found that close to 32 percent of Americans have
sought professional counseling for issues related to mental health. Given the prevalence of
disability in the United States, competent rehabilitation counseling services are essential;
however research about counselor trainees’ advocacy competencies is almost nonexistent
(Hudson, Shapiro, Ebiner, Berenberg, & Bacher, 2017; Waldmann & Blackwell, 2010).
In addition to the increasing number of people reporting disabilities and who participate
in rehabilitation services, there are economic, education and housing disparities between people
with disabilities (PWDs) and those without disabilities. These disparities represent oppression in
the form of unjust distribution of resources due to the stigma associated with disability and the
systemic barriers in place that have perpetually afflicted PWDs. Oppression is a societal concern
whether intentional or unintentional, these attacks can have staggering effects on the individual
and the community (Ratts, Singh, Nassar-McMillan, Butler, Rafferty, & McCullough, 2016).
The reported barriers, lack of accessibility and hardships related to employment, housing,
and education opportunities are concerning. In 2016, the data from Bureau of Labor Statistics
reported that among working age persons with disabilities, labor participation measured at 17.9%
and the rate for persons without disabilities was 65.3%. Other reports echo similar concerns in
areas of employment, housing, and poverty. The Center for Disease Control and Prevention

4
reported higher rates of unemployment for PWDs (13.9%) compared to people without (6.0 %),
poverty levels (22%) compared to (12.8%), violence (32.4%) compared to (21%), and higher
school dropout rates (23.5%) compared to (11%). Furthermore, females have less favorable
circumstances when compared to males. In regard to gender and disabilities disparities, it is
reported that women with disabilities are less likely to engage in management, professional,
related vocations (34.9% of women with disabilities compared to 41.8% of women without
disabilities) and were likely to earn below wages ($32,500) when working full-time when
compared to women without disabilities ($38,000) (Bureau of Labor Statistics, 2013). As a
result, PWDs are at increased risk for economic, health, housing and other problems. When
examining these disparities, it is obvious that PWDs have fewer opportunities compared to
persons without disabilities. Taking into account these trends, it is expected that a person with a
disability will experience hardship at some point in their life and require competent rehabilitation
counseling services. If these disparities among disability populations are not addressed,
problems related to quality of life and systems of oppression for PWDs will continue to increase.
It is critical that rehabilitation counselors engage in all levels of advocacy to challenge systems
of oppression that are counter- productive to the well-being of people with disabilities. To date,
there is a lack of research examining if pre-service rehabilitation counselors are prepared to
engage in advocacy at different levels and to fill this gap, the current study explored counselor
trainees competencies in six social justice advocacy domains.
The Rehabilitation counseling profession and related counseling professions is a vocation
dedicated to helping others. Professional counseling is described as a professional dynamic that
supports diverse individuals, families, and groups to achieve vocational, mental health and
wellness goals (ACA, 2014). Rehabilitation counselors assist people with physical, mental, or

5
developmental disabilities to achieve independence and to manage the psychological, vocational
and social aspects of disabilities (Bureau of Labor Statistics-Occupational Outlook Handbook,
2018). Leahy, Fong, and Saunders (2003) studied the practice of rehabilitation counselors and
found that certified rehabilitation counselors identified advocacy as their second most important
job function, more specifically, they engaged in social political advocacy, empowerment, and
community advocacy. The study also reported knowledge domains for rehabilitation counselors
to include knowledge of systemic and societal barriers that impede accessibility and equality for
people with disabilities. The study demonstrates that counselors have an important and unique
role in the lives of people with disabilities and are in a position to challenge stigma, prejudice
and advocate for people with disabilities (Thomas, Curtis, & Shippen, 2011). As long as the
field of rehabilitation counseling is committed to champion accessibility in all areas of life for
people with disabilities, social justice and advocacy will remain foundational in counseling
training (Chang, Hays, & Milliken, 2009). Considering the responsibilities and scope of practice
of rehabilitation counseling, counselors must have the ability to address social injustices faced by
their clients (Goodman, Morgan, Hodgson, & Caldwell, 2017; Miller & Sendrowitz, 2011; Ratts
& Hutchins, 2009). Thus, exploring the competency to engage in advocacy of counselor trainees
is important (Hudson et al., 2017).
In summary, engaging in advocacy is essential in counseling, yet few studies have
examined social justice advocacy competence in rehabilitation counselor trainees (Ratts &
Hutchins, 2009; Smith, Reynolds, & Rovnak, 2009), and the scarcity of research was the primary
catalyst for this study. To undertake this deficiency, the present study examined the relationship
between social justice advocacy competency and ethical awareness, in addition to exploring the
personal characteristics and counseling training of counselor trainees that may predict

6
competency in social justice advocacy. It was the intention of the study to gain insight of the
educational needs of counselor trainees.
Statement of the Problem
Given the growing prevalence of disabilities in the United States and the high rates of
poverty, unemployment and homelessness experienced by people with disabilities, providing
competent rehabilitation counseling services is critical. Social justice advocacy is necessary to
improve the quality of life for people with disabilities and rehabilitation counselors are in a
unique position to engage as social change agents, however; a review of the literature suggests
insufficient research examining the advocacy competencies of rehabilitation counselor trainees
(Decker, Manis, & Paylo, 2015; Goodman, Morgan, Hodgson, & Caldwell, 2017; Motulsky,
Gere, Saleem, & Trantham, 2014; Ratt & Hutchins, 2009; Waldmann & Blackwell, 2010).
Moreover, existing inquiry has examined the competency of counselor trainees from other
disciplines and not rehabilitation counseling (Bemak & Chung, 2011; Linnemeyer, Nilsson,
Marszalek, & Khan, 2018; Murray & Crowe, 2016; Ramirez Stege, Brockberg, & Hoyt, 2017),
while others have focused on whether interest and dedication predicts social justice advocacy
(Miller & Sendrowitz, 2011), or if courage and patience increases advocacy practices (Goodman
et al., 2018), and another study was interested in learning about the impact of counseling
curriculum integrated with topics of oppression and privilege (Hays, Dean, & Chang, 2007).
The rehabilitation counseling profession has adopted ethical and professional standards to
ensure social justice advocacy competency. For instance, counseling professional associations
like the Commission on Rehabilitation Counselor Certification (CRCC), the American
Counseling Association (ACA) and counselor education accreditation bodies such as the Council
for Accreditation of Counseling and Related Educational Programs (CACREP) have outlined

7
specific expectations and practices to carry out advocacy; yet, little is known if professional
standards and counselor training promote advocacy proficiency in rehabilitation counselor
trainees (Motulsky, Gere, Saleem, & Trantham, 2014, Ratt & Hutchins, 2009).
Social justice advocacy competency is critical in counseling and to pursue social justice
for PWDs, counselor training, advocacy skills and strategies are necessary (Smart & Smart,
2006). Thus, determining whether counselor training of pre-service rehabilitation counselors
predicts social justice advocacy competency was relevant to this study. To achieve the
aforementioned, counselor trainee preparation and advocacy training, in addition to demographic
variables and the relationship between ethical awareness and social justice advocacy competency
was examined.
Purpose of the Study
The purpose of the study was to investigate the social justice advocacy competencies of
rehabilitation counselor trainees. More specifically, counselor trainees’ demographic variables,
preparation, and advocacy training were examined to determine whether these variables
contribute to proficiency in advocacy. Also, the relationship between social justice advocacy
competency and ethical awareness was tested. In doing this, the study addressed gaps in the
existing body of literature in the field of rehabilitation counseling training. Furthermore, the
intention was to identify the educational needs of pre-service rehabilitation counselors that will
facilitate competency in social justice advocacy. Thus, the following research questions were
asked in this study:
Research Questions
The present study was designed to explore the competencies of social justice advocacy for
rehabilitation counselor trainees. Specific research questions are as follows:

8
RQ 1: How do counselor trainees rate their level of competency in social justice advocacy?
RQ 1.1: How do counselor trainees rank order the importance of each social justice advocacy
competency domain?
RQ 2: How do counselors in training rate their level of ethical awareness?
RQ3: What is the relationship between level of competency in social justice advocacy and ethical
awareness of counselors in training?
RQ3.1: Is there a significant relationship between each social justice advocacy competency
domain and ethical awareness of counselors in training?
RQ4: What personal characteristics (age, ethnicity, gender, sexual orientation, ethical awareness
and, disability status) of counselor trainee account for the level of competency in social justice
advocacy?
RQ5: What training (classification, internship experience, social justice advocacy course, and
counseling program) of counselor trainee account for level of competency in social justice
advocacy?
Significance of Study
There are a number of benefits in examining the social justice advocacy competencies of
rehabilitation counselor trainees. It is important because there is a lack of research focused on
social justice advocacy in rehabilitation counseling, specifically related to counselor trainees.
Previous research has focused on the practice and job functions of professional rehabilitation
counselors (Leahy et al., 2003; Leahy, Muenzen, Saunders, & Strauser, 2009). Additionally,
previous studies have targeted other counseling disciplines, thus, this study examined the
perceptions of rehabilitation counselor trainees to expand the counseling literature (Kilbane,
Freire, Hong, & Pryce, 2014). Thus, it was the intention of the current study to add empirical

9
evidence to the existing body of knowledge related to rehabilitation counselor trainees. Also,
social justice advocacy in rehabilitation counseling is a critical competency (Toporek, Lewis, &
Crethar, 2009) and it is the intention of the current study to outline implications for counseling
instruction, development of curriculum and training. Students, educators, accreditation bodies
and counseling training programs all can benefit from the current study as they gain insight of
what may foster training opportunities and overall student optimal learning outcomes. Findings
of the study may provide essential information to counseling education. Educators and
counseling programs may find the data useful to enhance their counseling curriculum including
course requirements, internship experience, and counseling theoretical perspectives. Finally, due
to the gaps in the current literature and the lack of empirical studies related to the advocacy
competencies of rehabilitation counselor trainees, there is a need for research to focus on a larger
and more diverse sample of counselor trainees (Beer, Spanierman, Green, & Todd, 2012).
Understanding the academic and training experiences of counselor trainees is an
important step to identify the strengths and needs of counselor trainees. In sum, results of the
study may provide insight and implications to rehabilitation counselor trainees, counselors,
educators, and researchers.
Definition of Terms
Social justice: the value of fair and equal distribution of resources, rights and treatment (Lewis
& Lewis, 1993).
Social justice advocacy: activism for social change, particularly with a focus on oppressive
societal structures and systems (Marbley, Bonner, Robinson, Stevens, Li, Phelan, & Huang,
2015).

10
ACA Advocacy competencies: a framework of counseling intervention and strategies that occur
on multiple levels in order to execute social justice advocacy. (Lewis, 2011; Ratts & Hutchins,
2009).
Ethical awareness: The capacity to resolve ethical or moral dilemmas with awareness of how
the action will impact those involved, actions are guided by three ethical dimensions (care,
justice, and critique) (Branson & Gross, 2014).
Counselor trainee: graduate student enrolled in a master or doctoral rehabilitation counseling
program or related counseling program.
Assumptions, Limitations, and Delimitations of the Study
The researcher assumes that the participants will provide truthful responses. The
researcher assumes questions and instruments are appropriate and measure what they are
intended to measure. Some limitations to this study should be taken into account in the
interpretation of the findings. For example, the participants for the study were self- selected and
volunteered; there is a potential sampling bias. The results are based on a sample of volunteers
and did not include data from counselor trainees who chose not to participate in the study. The
study will use a sample of participants from seven different universities. The results will be
limited to a small convenience sample size. Generalizability is a limitation of the current study
since a convenient sample will be used, therefore; cannot be applied to a larger population of
counselor trainees nationally. Another possible limitation is respondent bias. There is a potential
for participant to respond based on social desirability. Although the selection of participants may
limit the generalizability of the study findings; many of the findings may outweigh the
limitations where findings may be valuable and practical. A delimitation of the study is that only
students who are studying counseling in a Southwestern state will be included in this study.

11
CHAPTER II
REVIEW OF THE RELATED LITERATURE
Theoretical Framework
Chapter Two of this study is the literature review. The purpose of this chapter was to
review the literature in relation to social justice advocacy in rehabilitation counseling and the
competencies of rehabilitation counselor trainees. It begins with the theoretical framework
followed by social justice advocacy in rehabilitation counseling, and correlates of social justice
advocacy competencies.
A social justice perspective provides the theoretical framework for this study. Social
justice is viewed as foundational to activism and it is described as “distributive justice” or the
distribution of assets and burdens in society in order to promote fairness to all persons (Rawl,
1971). According to social justice theorist, Rawl (1971), a justice society is defined as one that
values the fair and equal sharing of goods to groups of greater need in society; emphasizing that
all members of society are afforded equal civil rights and duties. This means that everyone is
equal regardless of race, class, gender or status. Distributive justice is based on three dominant
theories: Utilitarian, libertarian, and egalitarian. Egalitarian theories which are aligned with a
social justice philosophy assert that all members of society warrant the same rights,
opportunities, and resources. Rawls (1971) expanded on the resource distribution and egalitarian

12
theories adding that each person merits both benefits and burdens not only by material goods
and services but in non-material goods and services including possibility and power. Scholars
have used this perspective to illustrate the societal responsibility to promote equity and harmony
(Fietzer & Ponterotto, 2015; Rawl, 1971). Justice must be accessible directly with individual,
community, and at institution levels in to achieve a fair and equal system for groups that
historically have been systemically marginalized (Fietzer & Ponterotto, 2015). Constantine,
Hage, Kindaichi, and Bryant (2007) also note barriers to full participation is often due to
environmental factors such as social attitudes, institutions, and policies, which lead to the
impairments of personal, vocational, and social development of marginalized groups. Finn and
Jacobson (2017) point out the most vulnerable members of society more often benefit from the
redistribution of societal resources. According to Crethar and Ratts (n.d.) equity, access,
participation, and harmony are four critical components of social justice with the intention to
promote distributive justice.
Social justice theory is foundational to the ACA advocacy competencies and the
competencies serve as a social justice advocacy framework for counselors (Ratts, DeKruyf, &
Chen-Hayes, 2007). Social justice advocacy is described as activism for social change and
entails taking action that is guided by the advocacy competencies of which are interventions and
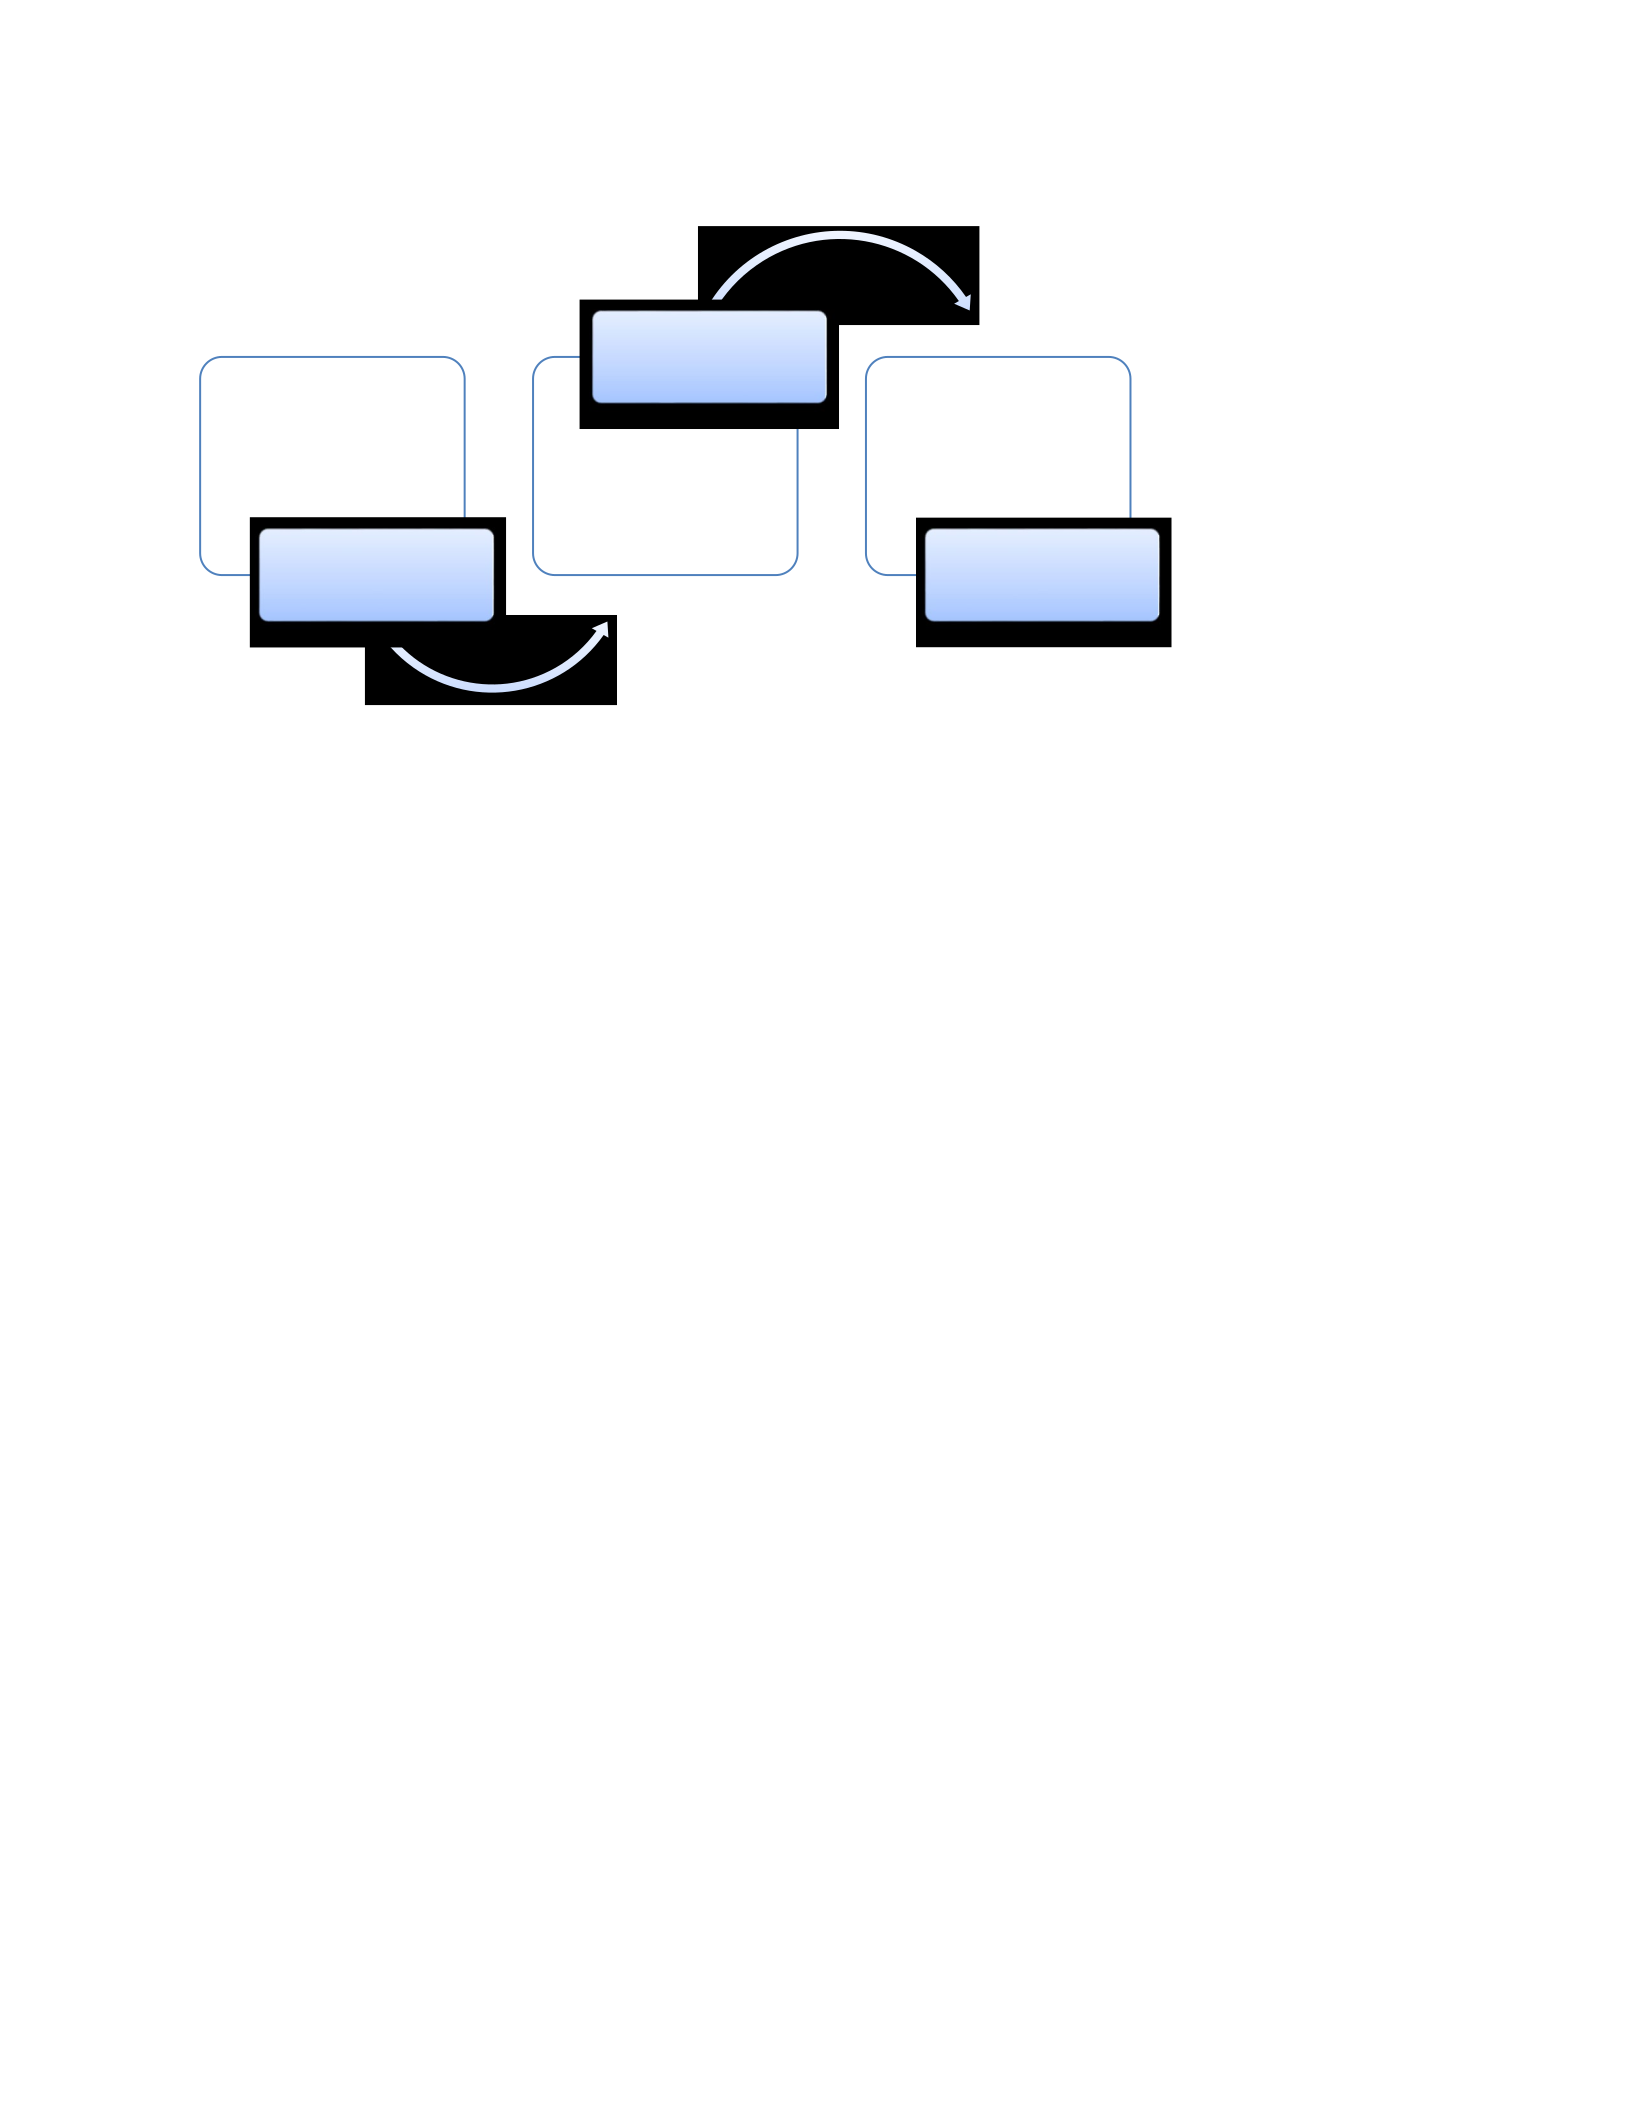
strategies based on social justice principles. Figure 1 illustrates the interaction of social justice
theory and the advocacy competencies of which provides a framework to engage in social justice
advocacy for rehabilitation counselors.
13
Figure 1: Social Justice Advocacy Framework (Rawl, 1971; Lewis, Arnold, House, & Toporek,
2002)
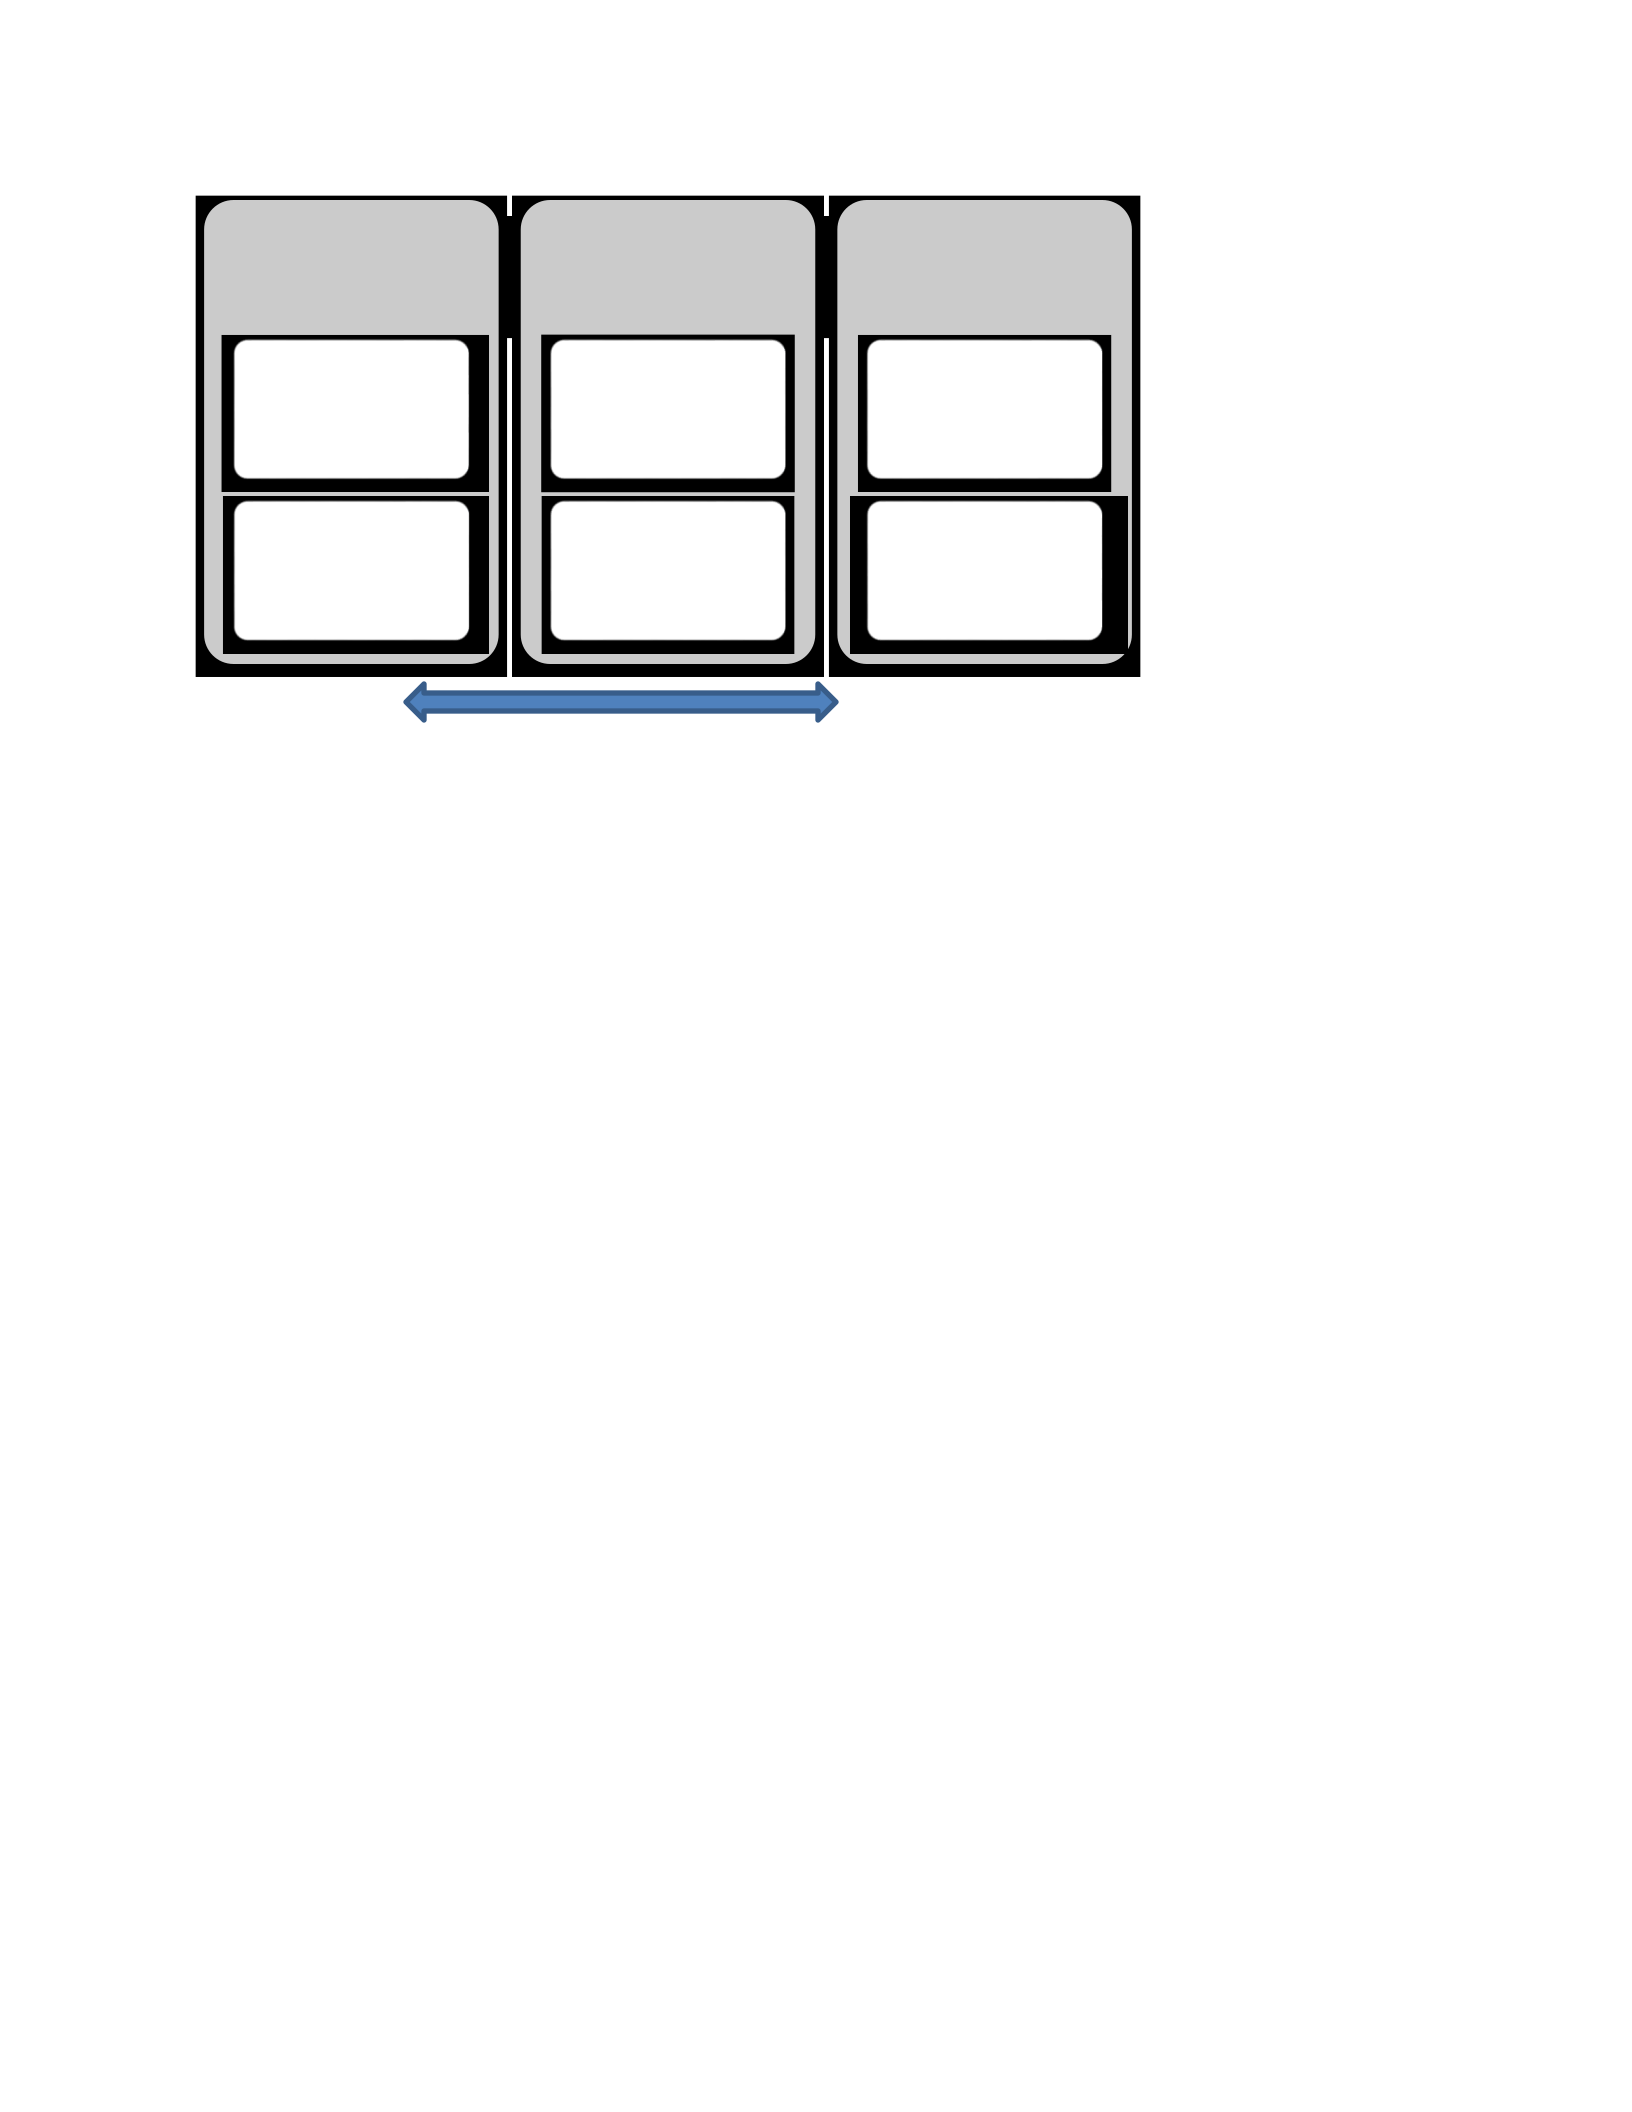
According to the ACA advocacy competencies, there are three levels of advocacy: a)
client/student advocacy, b) school/community advocacy, and c) public arena advocacy, and
counselors can engage in advocacy through direct interventions (micro level) or indirect
interventions (macro level). Each advocacy level encompasses two domains with specific areas
of and interventions. For example, the client/student advocacy level domains are client/student
empowerment and client/student advocacy. The interventions associated with the client/student
empowerment domain are as follows: identify strengths and resources of clients/students,
identify barriers that affect client/student, and teach self-advocacy skills to client/student. Figure
2 illustrates the ACA advocacy competencies which displays three levels of advocacy with two
domains in each level (Lewis, Arnold, House, & Toporek, 2002).
•Participation
•Harmony
•Equity
•Access
Social Justice
Theory
•Client Advocacy
•Community Advocacy
•Public arena Advocacy
ACA
Competencies •Empowerment,
Alliances,
Collaboration, Lobbying
•Systems analysis
Social Justice
Advocacy
14
Microlevel Macrolevel
Figure 2: ACA Advocacy Competencies (Lewis, Arnold, House, & Toporek, 2002)
Rehabilitation Counseling and Social Justice Advocacy
Professional Standards
Social justice advocacy is support by professional and educational associations. The
Commission on Rehabilitation Counselor Certification has established the Code of Professional
Ethics to promote caring and competent rehabilitation services to people with disabilities. As
such certified rehabilitation counselors are expected to act in accordance with the Code.
According to the Code, rehabilitation counselors have an ethical responsibility to engage in
advocacy for and with their clients (Code of Professional Ethics, 2017). Advocacy is
highlighted as an enforceable standard of ethical practice in rehabilitation counseling of which
counselors are expected to participate in advocacy at the individual, group, institutional, and
societal levels. More specifically, the following standards have been outlined to guide the
profession to execute advocacy and competent rehabilitation services: Section A: The
Counseling Relationship section A. 1.a. states “the primary responsibility of a rehabilitation
counselor is to respect the dignity of clients and to promote their welfare.” Section A. 2.b. states
Client/Student
Advocacy
Client/Student
Empowerment
Client/Student
Advocacy
School/Community
Advocacy
Community
collaboration
Systems
Advocacy
Public Arena
Advocacy
Public
Information
Social/Political
Advocacy

15
“rehabilitation counselors do not condone or engage in the prejudicial treatment of an individual
or group based on their actual or perceived membership in a particular group, class, or category.”
Section C.1. rehabilitation counselors recognize that disability frequently occurs in association
with other social justice issues (e.g. unemployment, poverty), therefore, “rehabilitation
counselor’s advocate at individual, group, institutional, and societal levels.” Section C:
Advocacy and Accessibility lists the following standards related to advocacy: a) rehabilitation
counselors engage in the removal of stigma and misconceptions of disability, b) empower clients
and their families when appropriate, c) perform organized advocacy, d) engage in systemic
change, e) understands the limitations of confidentiality and advocacy, f) awareness of the
systemic barriers to employment, education, housing, health care and more, g) knowledge of the
impact of systemic barriers to the quality of life.
The American Counseling Association (ACA) is a professional and educational
organization for professional counselors in various settings. The ACA established the Code of
Ethics to promote the compliance of counselors and counselors-in-training with the ethical
standards of professional counseling. Social justice and respect for diverse individuals, families,
and groups have been listed by the ACA as core professional values of the counseling profession.
Section A.7a. states that when appropriate, counselors engage in individual, group, institutional,
and societal levels of advocacy to remove the possible barriers to the wellness of the client. In
2003, the ACA endorsed the advocacy competencies to promote competent social justice
advocacy in professional counseling.
The Counselors for Social Justice is a division of the American Counseling Association
that was established to promote the duty of advocacy in professional counseling. Their mission
is stated as the responsibility of counselors to promote social justice through the empowerment

16
of individuals and groups as well as the engagement to reverse the inequality in society. They
further state that social justice advocacy principles are founded on the belief of accessibility and
equal opportunities for all members of society whether at the individual, community or systemic
level.
Counselor education accreditation bodies like The Council for the Accreditation of
Counseling and Related Educational Programs (CACREP) promote educational standards for
eight core areas of counseling and standards of instruction and supervised clinical experiences.
According to the 2016 CACREP standards of instruction for Clinical Rehabilitation Counseling
and Rehabilitation Counseling, social justice advocacy must be integrated in the counseling
program’s instruction, supervision, and training. To be in compliance with this expectation, the
following standards, which outline topics and interventions, have been established for Clinical
Rehabilitation Counseling: Standard 2.k., effects of discrimination, such as handicapism,
ableism, power, privilege, and oppression on clients’ life and development, Standard 3.c.,
strategies to advocate for people with disabilities. In regards to Rehabilitation Counseling:
Standard 1.e., principles of societal inclusion, participation, access, and universal design, with
respect for individual differences, Standard 2.e., impact of psychosocial influences, diversity and
social justice issues, poverty, and health disparities, Standard 2.f., impact of socioeconomic
trends, public policies, stigma, access, and attitudinal barriers as related to disability, Standard
2.n, advocacy on behalf of individuals with disabilities and the profession as related to disability
and disability legislation, Standard 3.j. advocacy for the full integration and inclusion of
individuals with disabilities including strategies to reduce attitudinal and environmental barriers.
Counselor professional and education bodies have clearly stated the significance of social
justice and advocacy competency in counseling, yet rehabilitation counselor trainee social justice

17
advocacy is relatively unknown. Waldemann and Blackwell (2010) point out to achieve
advocacy competency, rehabilitation counselors must acquire skills and knowledge that include
policy and social issues that impact their clients, but little research has been done to examine
rehabilitation counselor trainees’ advocacy competency.
Disability Advocacy
The conceptualization of disability has been influenced by social traditions, practices,
institutional and political factors (Myers, Jenkins Lindburg, & Nied, 2014Thomas, Curtis, &
Shippen, 2011). For instance, a medical perspective of disability posits that a physical or a
psychological impairment is the cause of disability and that it is a personal pathology (Goodley,
1997). The medical view describes disability as a tragedy of which causes dependency on others
and expects the individual to make personal adjustments to fit in with their environment. On the
other hand, a social view of disability explains that impairment is not synonymous with disability
and instead it is the physical environment and societal attitudes that must be adjusted to increase
independency and inclusion of people with impairments (Goodley, 1997, Smart & Smart, 2006).
The Americans with Disabilities Act (ADA) is a set of federal regulations that guarantees the
protection of the civil rights of people with disabilities in all aspects of public life (ADA gov).
The regulations appear to be influenced by both a medical and social view of disability. In the
text of the ADA, disability is regarded as a legal term and defines a person with a disability to be
an individual who 1) has a physical or mental impairment that substantially limits a major life
activity, 2) has a record of such an impairment, 3) or is regarded as having such an impairment.
Advocacy has had an important role in bringing awareness to disability rights issues.
More specifically, political advocacy has been successful in changing laws to include the
protection of the civil rights of people with disabilities with emphasize on accessibility and

18
equality. Political advocacy led by people with disabilities in protest of employment,
educational, and health care injustices began to take shape in the 1970s (Pelka, 2012). For
instance, in 1977 for more than two weeks hundreds of people with disabilities and their allies
led marches, sit-ins and occupied federal government buildings in New York, San Francisco, and
Washington to protest the pending regulations for section of 504 of the Rehabilitation Act of
which had been enacted in 1973 (Pelka, 2012). Section 504 regulations ensure the enforcement
of equal treatment and opportunity for people with disabilities in work, educational, and
recreational settings. Also, in 1977 and 1978 groups of disability advocates organized a public
demonstration in Denver and New York to change the lack of policy that guaranteed wheelchair
accessible public transportation and an accessible transit system (Pelka, 2012). Additionally,
political and social advocacy was responsible for the passage of the Americans with Disabilities
Act of 1990 (ADA). For more than two years, people with disabilities and their allies organized
and negotiated with legislators to ensure that a more comprehensive civil rights disability federal
policy was created. For the first time in US history, people with disabilities shared their personal
stories in front of law makers at public hearings and had a significant role in writing and securing
a policy that was more equip to address critical disability issues which had been largely ignored
by previous policies (Pelka, 2012). Despite the aforementioned events and progress in American
policy during this period, there continued to be significant societal barriers that guaranteed equal
participation of people with disabilities in America society, thus, shaping the disability rights
movement (Harris, Owen, & De Ruiter, 2012; Pelka, 2012). Many stories and disability
experiences shared directly from the individuals prior and during the disability rights movement
are recorded in Pelka’s (2012) book What We Have Done: An Oral History of the Disability
Rights Movement. His book illustrates the daily injustices that targeted people with disabilities

19
including denied or segregated public education and forced institutionalization; also, the critical
role disability advocacy had in the removal of disability stigmatization and the physical barriers
created by society. The social injustice and the rejection of human rights experienced by
individuals with disabilities set the tone for the disability rights movement in the 1960s
(Radermaher, Sonn, Keys, & Duckett, 2010). This mistreatment has been referred to as
Handicapism, which is the set of beliefs and practices that further the unequal treatment of
people on the basis of disability (Thomas, Curtis, & Shippen, 2011). The movement’s message
was that the problem was society’s refusal to accommodate and include people with disabilities.
For this reason disability rights advocates focus was to remove discrimination and oppression
and call for the equity of people with disabilities (Radermaher et al., 2010). Further, disability
activists argue that inclusion is not only a right, but there is economic, cultural and social value
on society when inclusive communities are in place. The implementation of inclusive
communities and the practice of equal participation of people with disabilities continue to be a
challenge. The social movement for disability rights that began in the 1960s gave a clear picture
of the important relationship between advocacy and the rights of individuals with disabilities.
A number of scholars from a variety of disciplines have written about the importance of
disability advocacy in removing the misconceptions of and the social marginalization of people
with disabilities (Alston, Harley and Middleton, 2006; Radermaher et al, 2010; Smart & Smart,
2006; and Thomas et. al, 2011). It is noted that social discrimination and the barriers to a healthy
quality of life of people with disabilities is more likely to be the result of societal disability
misconceptions and prejudice (Smart & Smart, 2006; Thomas et al, 2011). For instance,
individuals training to work with people with disabilities present with misconceptions about
disabilities. Thomas et al. (2011) asked graduate students enrolled in general and special

20
education teacher, rehabilitation, and counseling courses about their perceptions of different
types of disabilities. Although, in general attitudes and perceptions were positive, they found
that the discipline of study and the type of disability may have an influence on perceptions and
attitudes toward disabilities. Implications of the study suggest there is a lack of educational
opportunities to learn about disabilities and a value in integrating disability studies into
counseling programs to expand the skills of pre service counselors. Further, the authors
emphasize this is important since human service providers will be in a position to challenge
stigma, prejudice and advocate for people with disabilities. Radermaher et al. (2010) reports that
more needs to be done to correct the misconceptions related to people with disabilities. They
surveyed a disability advocacy organization that self identifies as inclusive with having
employees and board members who identify as a person with a disability and found the
organization to not be fully accessible to participation opportunities and when people with
disabilities did participate they were not recognized for it because their level of participation was
not viewed as equal to those who did not have a disability. In other words, people with
disabilities are visible and have roles at the organization; however, their efforts and their need of
supports are often ignored by those who do not have a disability which can be viewed as
perpetuating the misconceptions of disability.
The government supports the societal role to promote equal and fair opportunities for
people with disabilities. Reports such as the 2005 U.S. Surgeon General’s report titled “Call to
Action to Improve the Health and Wellness of Persons with Disabilities” highlights the
relationship of health to the quality of life. The report further states that with good health,
persons with disabilities have opportunities to work, learn and actively participate with their

21
families and their communities, and emphasizes that all members of society have an important
role in improving the overall wellness of PWDs.
Social Justice in Counseling
The tenets of social justice counseling support the integral principles of the counseling
profession: autonomy, fidelity, justice, non-maleficence, and veracity. A social justice
counseling perspective is described as an extension to traditional counseling views and practices
(Lewis, Ratts, Paladino, & Toporek, 2010). For instance, social justice counseling promotes
social justice ideals, describes mental and physical stability as a basic human right and considers
the implications of discrimination and oppression on a person’s quality of life (Chang, Crethar,
& Ratts, 2010; Lewis, 2011). The counseling interventions used are also an extension of
traditional ones with a focus on social action (institutional and social political) strategies and
activism, which fully address social barriers, instead of traditional interventions such self-
empowermen (Hipolitio-Delgado, Pharaoh, & Hemosillo, 2016; Ratts, 2009; Crethar &
Winterowd, 2012). Thus, a social-justice-minded counselor is described as a leader and systems
change agent who empowers individuals, families, and communities (Ratts & Hutchins, 2009).
Roysircar (2009) asserts that a social justice counselor is one that has a deep understanding of
social justice advocacy, knowledge of the history of social action, engages in social change and
recognizes the implications of the social system and political economy on its community.
Social justice counseling posits that optimal congruence for the client is achieved by
addressing both internal and external factors that impact the wellness of the client (Ratts &
Hutchins, 2009). This concept is based on the view that a person is the product of their
environment, therefore; difficulties are not always internally constructed (Ratts, 2009); both the
individual and the environment have influence on health and mental wellness (Chang et al,

22
2010). Another important facet of social justice counseling is the philosophy that both the
counselor and the client contribute to the change and intervention (Toporek, 1999) and client
participation throughout the counseling process is necessary to facilitate client empowerment and
equal access to opportunity (Lewis et al., 2011).
As described by Alston et al (2006) the aim of social justice counseling is to encourage
self-worth, self-determination, physical and psychological wellness through the distribution of
power and resources. Advocacy is used to promote social justice and social change. Crethar and
Ratt (n.d.) describe the view of social justice counseling as one that is grounded by the concept
of distributive justice and the belief in the common good in order to facilitate optimal mental and
physical human development. They present four principles that guide this counseling approach:
equity, access, participation, and harmony. Equity is the fair distribution of resources, rights,
responsibilities to all who are part of society. Access is the right to equal use of resources,
services, power, and information. The other two elements of social justice are participation and
harmony. Participation is regarded as the right to engage in the decisions that directly and
indirectly impact the individual. Harmony is described as the best possible outcomes for the
community as the result of actions from individuals or groups. This view is supported by
findings from a study done by Lewis et al. (2011), who conducted a workshop for counselors in
training, professional counselors and educators. They found that participants from the workshop
reported barriers to social justice advocacy stemmed from limited training, specifically, not
familiar with social justice counseling and advocacy concepts. Although many participants
reported advocating for their clients, they did now view themselves as competent social justice
advocates and suggested more needed to be done to change this barrier. Participants agreed that
more should be done by counseling professional organizations to promote social justice

23
advocacy training and assessment is necessary. This suggests that future leaders in the
counseling field will need skills and strategies to advocate for social justice and to further secure
advocacy within counseling.
Advocacy in Counseling
Toporek and Liu (1999) describe advocacy as a continuum of interventions ranging from
empowerment to social action used by a counseling professional to remove environmental and
systemic barriers of oppression impeding the clients’ well-being. Advocacy can occur on behalf
of the client such as the counselor representing the needs of the client or with the client in the
form of empowerment or self-advocacy. Advocacy is used to aid social justice and social
change. Advocacy is at the core of the counseling professional identity. In order to confront
social justice issues, counseling professionals have assumed a critical role as social justice
change agents. Social justice and advocacy are at the core of counseling and counseling
professionals have an ethical obligation to advocate for their clients. This means a push to
implement advocacy and social justice in counselor education and training has been expressed.
Advocacy can be defined as an “action on behalf of an aggrieved individual, group or
class of individuals—people subject to discrimination and injustice (Richan 1973, p.233).” As
advocacy is a significant function of the counseling profession and counselor programs have
established curriculum standards it is important to learn about counselor trainees’ competency in
advocacy while they are in counseling programs. It is common in traditional counseling to focus
on the individual an approach that significantly ignores the systemic issues that perpetuate
marginalized groups. Social justice advocacy can improve traditional counseling approaches
when working with people with disabilities and other diverse groups.

24
Scholarly discussion and research to better understand advocacy in counseling is
extensive; some of literature dates back to the late 1800s (Smith et al., 2009). The concept of
advocacy in counseling is significantly influenced by community counseling and multicultural
counseling, but is different since a purpose of advocacy counseling is to promote sociopolitical
change that has greater influence on the needs of the client (Kiselica & Robinson, 2001). With
this in mind, counselors are in an ideal position to engage in advocacy because of their training
in collaboration, leadership, consultation and advocacy (Lewis et al., 2011). The aforementioned
demonstrates the importance of exploring the competencies of pre-service counselors. Leahy’ et
al.’s (2009) study illustrates the importance of advocacy competency in rehabilitation
counseling. Their research asked rehabilitation counselors to report important knowledge
domains and the frequency in which they used the domains in order to meet the demand of their
work. The data provided by the study supports the established scope and training needs of
rehabilitation counseling students in training and professionals. The study surveyed a total of
648 Certified Rehabilitation Counselors, of whom more than 35 % reported they had a job title
of rehabilitation counselor while 13% stated they had a title of rehabilitation
consultant/specialist, and 3% reported they are employed as university educators. Seventy three
participants identified as female and 27% were male. Participants reported knowledge of
advocacy for people with disabilities is moderately important to improve outcomes for
rehabilitation clients and the frequency of advocacy in rehabilitation was ranked among the next
most used knowledge subdomains. Also, sixty eight percent of participants indicated that
advocacy skills to support the needs of people with disabilities should be acquired during
counselor training. The study suggests advocacy for people with disabilities is important in
rehabilitation counseling. These findings were also supported by another study by Waldmann

25
and Blackwell (2010) who after a review of the literature indicated the significance of advocacy
in counseling. They also highlight the updates and changes that were made to the Code of
Professional Ethics for Rehabilitation Counselors. As noted in the Code of Professional Ethics
for Rehabilitation Counselors (2017), rehabilitation counseling values “advocating for the fair
and adequate provision of services, respecting human rights and dignity, and promoting
empowerment through self-advocacy.” It further outlines the role of the rehabilitation counselor
to recognize advocacy occurs at the individual, group, institutional, and societal levels to
improve equal opportunity, accessibility, and the quality of life for persons with disabilities.
Rehabilitation counselors are expected to be knowledgeable in policies, laws, and systems that
influence accessibility to medical care, mental health care, employment, education, housing, and
transportation for persons with disabilities (Section C.1 f. of the Code of Professional Ethics for
Rehabilitation Counselors, 2017).
Advocacy Competencies
In response to the growing importance of advocacy in counseling, the American
Counseling Association (ACA) adopted and endorsed the Advocacy Competencies in 2003
(Lewis, Arnold, House, & Toporek, 2002). Soon after the division of Counselors for Social
Justice and the 2016 CACREP standards also endorsed the Advocacy Competencies (Lewis et
al., 2002) to demonstrate their support of social justice and advocacy in counseling. In
counseling, advocacy competency is defined as the ability, understanding, and knowledge to
carry out advocacy ethically and effectively (Toporek, Lewis, & Crethar, 2009). The catalyst for
the endorsement was to help counselors conceptualize advocacy with a social justice advocacy
framework. The advocacy model provides clear interventions and skills that can be used by
clinicians, supervisors and educators to execute competent social justice advocacy practice,

26
supervision, and training for the counseling profession. In using the competencies the
counseling professional is able to execute social justice in their practice at the individual and
systems level. In other words, the Advocacy Competencies were created to help conceptualize,
formalize, and facilitate social justice advocacy in counseling (Lewis et al., 2002; Ratts &
Hutchins, 2009). The Advocacy Competencies can be used as a model of which describes three
levels of advocacy. Each level includes two domains for a total of 6 domains with specific
competency areas and interventions to engage in advocacy. The Advocacy Competencies are
organized on a continuum that begins with micro interventions then moves to messo
interventions and ends with macro interventions. A micro level intervention reflects one that is
the most common in counseling, which is directly working with or on behalf of a client or
family. A meso level intervention is described as working with small groups such as a school or
community. A macro level intervention is one that involves the counselor to engage in large
systems as in social policy or lobbying. Also, the advocacy competencies are structured in a way
that guides the counselor to 1) determine whether the counselor will engage in advocacy on
behalf of the client (indirect interventions) or with the client (direct interventions) and 2)
determine the degree of advocacy engagement, micro, meso, or macro level. The client/student
empowerment domain involves direct interventions/counseling such teaching the client self-
advocacy skills. The counselor is acting with (works directly) the client and requires skills that
will help identify strengths and resources of client, train client to develop self -advocacy skills,
help clients develop and carry out self -advocacy action plans. The client/student advocacy
domain calls for advocacy interventions on behalf of the client or groups (work indirectly) who
lack accessibility to needed service. The counselor has the skills to negotiate, plan, and gain
access to needed resources for the client. The counselor must be equipped to identify barriers to

27
the well-being of the client, develop and carry out an action plan to confront identified barriers.
The community collaboration domain refers to counseling interventions of which the counselor
engages and collaborates with community in order to address social issues (Toporek et al., 2009).
In this domain, community can refer to a neighborhood, a church, or school in other words a
group. The counselor engages directly with the community and takes the role of an ally. As an
ally, the counselor offers experience, expertise, and integrity (Toporek et al., 2009). Important
skills for the counselor include communication, interpersonal relations, training and research.
Additionally, the counselor has the ability to identify environmental issues that interfere with
accessibility and the clients’ well-being. Competencies in this domain include the skills to create
alliances with groups who work for change, recognize environmental issues that hinder personal
growth of the client and to engage with the community. In this context, environmental system
refers to family, school, place of employment, neighborhood, or church (Lopez-Baez & Paylo,
2009). The systems advocacy domain describes advocacy as the counselor adopting a leadership
role in systems change at the community level (meso). Advocacy actions in this domain are
done on behalf of the client and their community. For example, the counselor represents their
client and may speak on behalf of the client and does not require the participation of the client
(Toporek et al., 2009). Eight advocacy competencies are presented that effectively remove
systemic barriers that impede client’s development. These include (a) distinguish environmental
issues interfering with clients’ development; (b) give and discuss data to demonstrate the need
for change; (c) in working with others, create a vision to direct change; (d) assess the cause of
political power and social affect within the system; (e) create a detailed plan for executing the
change process; (f) generate a plan to respond to possible reactions; (g) cope with resistance and
(h) evaluate the impact of counselor’s advocacy efforts on the system and constituents. The

28
public information domain indicates the counselor participates and engages in community
advocacy. An example of public information advocacy intervention is facilitating a public
meeting that presents awareness to social barriers that deters human worth and growth (Toporek
et al., 2009). The associated interventions and skills include the ability to collaborate with other
professionals, disseminate information via written and multi-media materials and assessing one’s
efforts. A counselor who has achieved competency in this domain is able to organize a public
information campaign with the community to inform the general public of an issue that impacts
the community at large (Toporek et al., 2009). A focus of the social/political advocacy domain
is policy change at a large scale and public level. Domain intervention implies the counselor
understands patterns of systemic injustices that can only be resolved through policy mediation
(Toporek et al, 2009). The counselor’s role is to engage in advocacy actions on behalf of
(indirectly) the public to eliminate macro level issues and barriers. Social/political interventions
include the ability to join with potential allies, support existing alliances for change, lobby law
makers and legislators and prepare data to promote change. According to the advocacy
competencies, advocacy means to engage in advocacy with the client or on behalf of the client
and describes advocacy to occur on three levels.
In summary, Ratts and Hutchins (2009) assert the advocacy competencies provide a
concrete framework, clinical implications, and suggest counselor training programs that integrate
this model help develop social justice advocacy oriented clinicians. Furthermore, they bring the
meaning of social justice counseling from theory to practice (Lewis, 2011) and can be utilized
with diverse counselor trainees, clients and communities (Brady-Amoon, 2011; Ratt et al., 2016).

29
Correlates of Social Justice Advocacy Competencies
A review of literature revealed research that examined the relationship between social
justice competencies and demographic variables and counselor training. The findings are
presented in the following section.
Ethical awareness
For the purpose of this study ethical awareness is defined as the capacity to resolve
ethical or moral dilemmas with awareness of how the action will impact those involved.
According to Gillian (1995) ethical decisions or moral dilemmas are guided by the following
three concepts: ethic of care, ethic of critique and ethic of justice. She describes ethic of care as
solving and reasoning based on the current scenario, the individuals involved in the scenario and
the bond of those involved. The ethics of care perspective is motivated by the bonds that people
create and the value of caring for others (Robertson & Walter, 2007). The ethic of justice refers
to resolving ethical dilemmas in terms of the justice approach where rules and standards are used
to reason the action.
Professional ethics are views about comportment that represent professional practices.
As cited in Branson and Gross (2014), ethical behavior in relation to leadership means the leader
is an individual of courage and integrity who is motivated and committed to doing the right thing
regardless of the consequences. As defined in Branson and Gross (2014), “ethical action skills
include “resolving conflicts, taking initiative as a leader, asserting respectfully, planning and
implementing decisions.” This definition is aligned with counseling professional duties. They
further state, there is an expectation for counselors to be ethical leaders meaning to act fairly and
promote good instead of harm. Ethical leadership is gained, learned, and is more than knowing
what it means instead how to act ethically, and having the desire to be ethical. Additionally,

30
when the practice of ethical leadership becomes deeply meaningful to the person, it becomes
more than a learned skilled, it become part of their character. The counseling profession has
adopted ethical standards to protect clients and guide professional behavior and ethical codes for
interpreting specific forms of conduct for the profession (Calley, 2009).
Ethics in counseling is an important competency and is outlined in professional
counseling standards. Counselor training standards for education programs have been set by
accreditation bodies like the Council for Accreditation of Counseling and Related Educational
Programs (CACREP). For example, ethical considerations and practices are identified as one of
eight core areas that must be included in the curriculums of counseling education programs.
Professional counseling organizations such as Certified Rehabilitation Counselors (CRC) and the
American Counseling Association (ACA) have each adopted a code of ethics to facilitate ethical
awareness, obligations, and practices for counselors, supervisors, and counselor trainees.
According to the ACA Code of ethics (ACA, 2014) counselor trainees, counselor educators, and
practitioners all are held to the same standards. Cartwrights and Hartley (2016) investigated
ethics consultation in rehabilitation counseling, more specifically their study provided data about
the content of the advisory opinions made by the Ethics Committee of CRCC. They found that
most of the advisory opinions addressed ethical standards associated with the counseling
relationship, confidentiality, resolving ethical issues, and professional responsibility. This
suggests although a Code of Ethics for rehabilitation counselors are in place there may be gaps in
ethics education and training.
Ethical awareness in counseling has been investigated. Landon and Schulz (2018)
investigated the perception of supervisors’ and their role in counselor ethical awareness. The
study found that using a “supervisor working alliance” approach with counselor trainees

31
improved the development of ethical awareness among their supervisees. This approach
integrates training, practical application case conceptualization, and mentorship. The findings
suggest comprehensive supervision facilitates ethical awareness. Another study examined the
relationship between ethical decision making and the characteristics of the counselor. The study
findings suggested there was not a significant relationship between ethical decision making and
personal characteristics (age, gender, and school counseling experience) of school counselors
(Lambie, Ieva, Mullen, & Hayes, 2011). However, another study noted that the variables gender
and the years of experience of a mental health professional did influence the ethical decision
making process (Walton, 2007). Mason and McMahon (2009) examined the influence of age,
gender, professional training, experience and school setting on the leadership practices of school
counselors. Leadership practices were measured and participants scored highest on the enable
others to act subscale and lowest on the inspire a shared vision subscale. Results indicated
participants who scored higher on all or most subscales of leadership practices where counselors
who reported more experience, or identified as having more years at their current school or were
older. The study reported a relationship with leadership practices with age and years at current
school on the five subscales and that age predicts practices of Inspire a Shared Vision, Challenge
the Process, Enable Others to Act, and Encourage the Heart. Mason and McMahon (2009)
concluded school counseling leadership depends on age, experience and size of the school
setting. Based on the results, they suggest that the role of leadership in counseling may not be
emphasized or clear and recommend counselor education programs examine curriculum to
include leadership development and identity in addition to understanding the implications of
leadership skills in counseling. Langlois, Lapointe, Valois and de Leeuw (2014) studied the
characteristics of school leaders in relation to ethical orientation. Specifically, the study

32
provided data on ethical conduct, ethical leadership training, and assessing ethical leadership.
They explain ethical leadership based on Starratt’s tridimensional model which is made up of
three interdependent dimensions of ethics (justice, critique, and care). These studies examined
personal characteristics of professionals in education settings, so the present study will add to the
literature as researcher is interested in examining counselor trainees enrolled in specialized
counseling training programs. The influence of ethics education on rehabilitation counseling
students has been examined (Tsai, 2013). The study found ethics education mostly consists of a
structured course that typically utilize the CRCC Code of Ethics and the ACA Code of Ethics as
training material and teaching method is heavily based on lecture method. In regards to the
rating of their ethics education and ethics competency, student reported they were moderately
satisfied with their training and reported ethical awareness confidence and competence to be
moderate. A limitation reported in this study was regarding the small sample used. A
recommendation noted in the study was to integrate more case study discussions, role play and
more classroom activities in addition to the code of ethics in order to facilitate competency in
resolving ethical dilemmas.
Counselor Training
To understand counselor trainees’ development of social justice competency, it is
important to examine counseling training and education that may account for such development
(Hudson, et al, 2017). In investigating the influence of counseling training on competency,
Goodman et al. (2018) found that comprehensive (full academic year) training that incorporates
microlevel advocacy coupled with collaboration, emotional support, and critical reflection not
only increases motivation to engage in advocacy, but participants reported their competency
increased as a professional counselor.

33
Holmberg-Abel (2012) studied the advocacy competency of professional school
counselors. The findings suggest that counselors engage in the advocacy level where they
perceive to be “very much to extremely” prepared and view as “very important”. More
specifically, more counselors viewed client/student advocacy as “very important” compared to
public arena/level as “important.” It is important to note that client/student advocacy refers to
empowerment, whereas, public arena/level refers to systemic advocacy. The sample reported
they are “very much to extremely prepared” to engage in client/student advocacy compared to
the other levels. This suggests that education and training focused on client/student advocacy.
Stackhouse-Powe (2014) also discovered that social work students enrolled in an accredited
social work program do not engage in political/system advocacy and suggested this was due to
the lack of social justice advocacy integrated in their training and field practice.
Decker et al. (2015) assert counseling programs must consistently present the role of
advocacy so that it becomes part of the counselor’s professional identity. In addition to
knowledge of multicultural theories, other theories such as social change, empowerment, and
advocacy theories must be explored by student trainees. Finally, field experience, volunteer
opportunities and reflective exercises promote advocacy to become part of a counselors’
professional identity. For example, an activity such as writing a letter to a local or state member
of government about oppression promotes social justice action.
Students report adequate training improves advocacy competency. Researchers evaluated
a case based collaborative learning model as a teaching tool for advocacy (Kilbane, Freire, Hong,
& Pryce, 2014). Masters-level clinical social workers self- rated their values and practices of
advocacy after their participation at Advocacy Week workshops that included discussions on
policy and clinical practice and legislative advocacy skills and faculty led case presentations

34
which are used for student reflection on context cases and clinical practice. Results indicated
this model benefited the students as a tool for teaching advocacy, specifically, policy
participation help promote the relationship between advocacy and clinical practice. The
researchers caution the implications of the study given the small sample size
Topics of privilege, oppression, and advocacy are important in curricula and during
supervision to improve counselor competency (Hays, Dean, & Chang, 2007). A qualitative
study explored the academic and clinical experiences of counselors from a variety of counseling
disciplines. Some questions proposed to participants included: “Based on your experiences,
what are some suggestions for training programs to facilitate discussions about privilege and
oppression issues?” If relevant, in what ways do privilege and oppression effect counseling
practice and/or training?” Participants of study reported a challenge they encountered as
counselors was the inability to address the experiences of discrimination and social injustices of
their clients. They further reported a lack of these topics during counseling preparation and
training.
Counseling training programs in the field of psychology have examined the role of
advocacy within the field and among students in training. A nation-wide survey by Ramirez
Stege, Brockberg, and Hoyt (2017) sought to learn how clinicians in training perceive their
advocacy competency. Specifically, the study examined the influence of advocacy resources,
advocacy engagement, and perceived importance of advocacy on advocacy competency. A total
of 188 participants selected from APA-accredited counseling psychology doctoral programs and
clinical mental health counseling –CACREP accredited master’s programs participated in the
study. Results indicated that participants who reported higher advocacy self- efficacy also
reported more accessibility to training and/or resources such as volunteer opportunities.

35
Additionally, a significant relationship was found between perceived importance and self -
reported advocacy competency. For example, participants who reported advocacy is “very
important” for the counseling profession had a significantly higher mean score versus
participants who reported advocacy is “important.”
The perceptions of doctoral psychology counseling trainees regarding social justice
interest and commitment were studied by Miller and Sendrowitz (2011). They asserted the
program training environment indirectly predicted social justice commitment and personal
morality is indirectly and directly significant in determining social justice commitment.
Furthermore, they found a large number of trainees reported highly motivated to engage in social
justice advocacy; however, they also indicated a lack of resources, time and direction from their
counseling program imperative for competency of social justice advocacy. Miller and
Sendrowitz (2011) suggest future research assess the interest and commitment to social justice
advocacy of counselor trainees from diverse populations and programs.
Bemak and Chung (2011) report the significance of counseling training programs that
include social justice counseling and advocacy concepts and practice in every facet of the
curriculum. Specifically, students who complete action oriented activities and practicum field
based training referred as “classrooms without borders” along with supervision and mentoring
report increased motivation and confidence about their advocacy skills and abilities.
Another study that examined the correlates of social justice advocacy among clinical,
psychology counseling and school psychology doctoral trainees found that discrimination,
multicultural knowledge, and multicultural awareness were statistically correlated with social
justice advocacy. The authors suggested that the relationship between experiences of
discrimination and engaging in social justice advocacy is influenced indirectly by a persons’

36
political involvement (Linnemeyer, Nilsson, Marszalek, & Khan, 2018). The study also
examined social justice advocacy differences among the three different counseling programs and
found no statistically significant differences among the programs.
A dissertation examined the social justice advocacy competencies of rehabilitation
counselor trainees in CORE accredited rehabilitation counseling programs. The participants
included Master level students enrolled in an internship course and full time faculty of CORE
accredited RCE programs. The results indicated that students reported more developed social
justice advocacy competencies in client advocacy and client empowerment with the least
developed in systems advocacy, public information and social/political advocacy. Faculty
results were similar to the students’; faculty reported that students have the highest competence
in client advocacy and the lowest in systems advocacy public information and social/political
advocacy. The study also reported a higher mean score for male students compared to female
students; however, no significance differences in gender, racial/ethnic background or age of
students was documented. Future research recommendations included comparing CORE
standards with teaching standards and exploration of reasons why counselor students report
limited competencies in systems advocacy and community collaboration (Jeon, 2014).
The literature reveals that previous research has focused on other disciplines such as
social work and psychology. The literature also suggests training and education is important for
the development of social justice competencies. It demonstrates that education and training must
incorporate social justice advocacy at multiple levels and throughout instruction to prepare future
counselors as competent social justice advocates. Furthermore, initial research indicates social
justice training is important, however; it is underdeveloped in numerous programs.

37
Counselor trainees’ demographic variables
To understand the development of advocacy competence of counselor trainees, personal
characteristics must be considered. To understand counselor trainees’ development of social
justice competency, it is important to examine the personal characteristics that account for such
development. In investigating factors that predict social and political advocacy, Goodman et al.
(2018) found in the literature review advocacy requires specific elements such as information,
motivation, allies, patience, courage, and training. The authors stress along with motivation,
gathering facts and information, learning important terms, and relevant stories are crucial for
effective advocacy. Other important advocacy skills include creating allies and building
relationships with others who share the same social justice concerns and view. They further state
advocacy necessitates courage to command change and is best effective when it is presented by
impassioned groups with comprehensive facts that support the cause.
The relationship between advocacy competencies and the characteristics of counselor
trainees has been explored in research studies. For example, Miller and Sendrowitz (2011) found
that personal morality is indirectly and directly significant in determining social justice
commitment among doctoral psychology counseling trainees. According to Beer et al. (2012),
who examined the commitment to social justice issues among Master and doctoral counseling
psychology students, found gender was correlated statistically with social justice commitment,
however; gender did not have a significant relationship with activism orientation and confronting
discrimination. Overall, the study suggests little significance for the role of social identity in
predicting social justice commitment among the counseling students. Another study found there
was no statistically significant racial and gender differences in counselor trainees’ level of social
justice advocacy engagement, more specifically in any of the following types of advocacy:

38
collaborative action, social/political advocacy, client empowerment, and client/community
advocacy (Luu, 2016). This study further reported that majority of participants identified as
White and as female. It also reported that White trainees had significantly more unawareness of
blatant racial issues than trainees of color. Also White trainees experienced less racial injustice
and witnessed significantly less racial injustice happening to others around them verses trainees
of color. However, there was no statistically significant difference between White trainees and
trainees of color with regard to their unawareness about racial privilege and institutional
discrimination. Trainees who experience and/or witness racial discrimination and gender
discrimination or more likely to participate in social justice advocacy. Also, results reported a
significant and positive relationship between participation in formal campus experiences (course
work, events) and trainees’ social justice advocacy behaviors. Study recommends that students
be given more opportunities to engage in experiential activities and for these activities to be
integrated into the campus community in order to increase social justice advocacy participation.
Wendler and Nilsson (2009) explored whether cognitive complexity and social political
advocacy predicted universal diverse orientation (UDO) among counseling psychology and
counselor education trainees classified as master level and doctoral students. UDO is described
as the recognition and acceptance of all people regardless of the similarities and the differences.
Overall, participants who were engaged in sociopolitical advocacy scored higher levels of UDO.
Doctoral level participants scored higher regarding UDO. They discovered significant group
differences between lesbian, gay or bisexual (LGB) and heterosexual participants on actual and
desired social political advocacy. Participants who identified as LGB had higher scores
compared to the participants who identified as heterosexual. In other words, students who
identified as LGB reported higher scores in the intention to engage and more time engaged in

39
advocacy activities. The researchers found it interesting since the LGB group was a much
smaller sample than the heterosexual group. It is important to report, a review of the literature
resulted little exploration of LGB status with regard to social justice advocacy competency.
Hipolitio-Delgado, Pharaoh, and Hemosillo (2016) did a qualitative study with two
graduate students, two high school counselors, one college counselor and one retired counselor.
All counselors identified as White, five identified as female and one identified as male. The
study found that the duty to advocate was reinforced when injustices where viewed first hand at a
personal level. Additionally, mentorship aided in their likelihood to engage in advocacy. They
recommend counselor educators and education programs provide learning activities and
internships that aid in hands on opportunities at underserved communities.
A qualitative study by Hoover and Morrow (2016), examined how mental health
counselors in training developed as social justice advocates during a feminist multicultural social
justice oriented practicum. The study found that participating in a social justice –oriented
training supported trainees’ development as it involved intrapersonal, interpersonal and
sociopolitical training opportunities. Participants reported social justice efforts such as self-
examination of their oppressed and privileged identities and doing social justice work during
their training had a significant role in their development. In other words, counselor trainees’
social justice development is likely fostered by training that involves personalizing social justice
and activism. All participants identified as women and 13 participants were doctoral students
from clinical or counseling psychology, 4 were students from master’s programs in social work
and 3 were students from master’s programs in professional counseling. They note that social
justice training in counseling is relatively new in its development and merits further research in
trainees’ awareness about their training experiences.

40
Feldwisch and Whiston (2015) examined the beliefs, attitudes and practices of social
justice advocacy for school counselors. Participants were practicing counselors with a Master’s
degree in counseling or a related field such as education or social work that is endorsed by
school counseling. The study indicates that counselors report moderate to high social justice
advocacy attitudes and moderate degree of social justice advocacy. Specifically, the study
suggests that school counselors from recognized comprehensive school counseling programs
scored higher on measures of social justice advocacy when compared to school counselors in
non-recognized school counseling programs. In other words, counselors who work at a school
that participates in a comprehensive program that aims to close the gap on achievement are more
likely to be advocacy action oriented.
Another study examined the direct and indirect relationships between social justice self-
efficacy, social justice commitment, social justice social support, social justice interest, belief in
a just world, and belief in an unjust world among graduate trainees from disciplines including
counseling psychology, marriage and family, addictions, school psychology and school
counseling (Inman, Luu, Pendse, & Caskie, 2016). The study revealed that social justice self-
efficacy beliefs had a significant and direct relationship with interest and commitment. The
study also suggested that interest in and commitment to social justice advocacy is less likely if
the individual believes justice already exists and members of society get what they deserve.
Another worthy finding was that counselor trainees’ confidence to engage in social justice work
increased with social support.
After review of the current literature on social justice advocacy competency in relation to
counselor trainees, it was noted that almost no research has focused on the rehabilitation
counseling field. In spite of professional standards and responsibilities and need for competent

41
rehabilitation services for people with disabilities, little is known if pre-service counselor are
prepared to engage in social justice advocacy. Empirical research can provide insight to the
strengths and needs of rehabilitation counselor trainees (Hudson et al, 2017; Miller &
Sendrowitz, 2011). Therefore, the current study explored variables such as counselor training
and advocacy training of counselor trainees’ in addition to the relationship between ethical
awareness and social justice advocacy.
Expected Outcomes of the Study
It is expected that current empirical study will add to the literature and will be
informative to students, researchers, educators, and counseling supervisors as they continue to
promote, guide, and implement social issues and advocacy in counseling training. It is
anticipated that current study will demonstrate support for the social justice advocacy
competencies as essential in counseling training given that some express uncertainty about the
application and benefits of mandating advocacy engagement in counseling (McLaughlin, 2009).
Additionally, it is the intention of the study to investigate the strengths and training needs of pre-
service counselor so that implications for best practices in social justice are expected to be
presented as currently there is a lack of such data (Ratts & Hutchins, 2009; Smith, et al., 2009).

42
CHAPTER III
METHODOLOGY
The following chapter describes the methods and procedures that were used to carry out
the present study. The chapter provides details about the participants, instruments used, method
and procedures of collecting the data, and methods of the data analysis. The purpose of the study
was to explore rehabilitation counselor trainees’ self- reported competency of social justice
advocacy. The study was designed to examine demographic and counselor training variables
that may predict social justice advocacy competency. The study was guided by the following
research questions:
RQ1: How do counselor trainees rate their level of competency in social justice advocacy?
RQ1.1: How do counselor trainees rank order the importance of each social justice advocacy
competency domain?
RQ2: How do counselors in training rate their level of ethical awareness?
RQ3: What is the relationship between level of competency in social justice advocacy and ethical
awareness of counselors in training?
RQ3.1: Is there a significant relationship between each social justice advocacy competency
domain and ethical awareness of counselors in training?
RQ4: What personal characteristics (age, ethnicity, gender, sexual orientation, disability status,
ethical awareness) of counselor trainee account for the level of competency in social justice
advocacy?

43
RQ5: What training (classification, internship experience, social justice advocacy course, and
counseling program) of counselor trainee account for level of competency in social justice
advocacy?
Participants and Sample
The participants of this study were recruited from rehabilitation counseling programs at
seven public universities in a Southwestern state. The targeted participants were master level
and doctoral level counselors-in-training enrolled in a counseling program. To improve sample
size, participants from one West coast university and one Midwestern university were recruited,
as well. In addition to graduate rehabilitation counseling programs, other counseling-related
disciplines, such as counseling psychology, social work, educational psychology and counselor
education were included. There is a small number of master and doctoral students in counseling
programs so limiting screening criteria was not used for the sample selection in order to secure
adequate data to achieve a certain level of statistical power in the data analysis. The participants
of this study volunteered, were recruited from various counseling programs, thus, are considered
a convenience sample. A convenience sample is made up of participants who are readily
available and may be representative of the population that is accessible for the data collection
process (Creswell, 2013). A limitation with this type of sample is that it may not entirely reflect
the targeted population and may generate biased results.
Power analysis
A power analysis was conducted to determine the required sample size to yield a given
power. The G*Power software was used to conduct a priori power analysis to determine the
appropriate sample size. It was determined that a stepwise multiple linear regression analysis
was appropriate for Research question 4, thus a power analysis was used to determine the

44
appropriate sample size. A nominal power of .90 was used and this means that with 90%
confidence that the effect can be detected. Power analysis for Research question 4 for a multiple
linear regression with six predictors was conducted in G* Power 3.1 to determine a sufficient
sample size using an alpha of 0.05, a statistical power level of .90, and a medium effect size .15;
based on this calculation the desired sample for this study is 123. A medium effect size of .15
or higher was determined to be appropriate (Cohen & Cohen, 1993). It was determined that a
stepwise multiple linear regression analysis was appropriate for Research question 5, thus a
power analysis was used to determine the appropriate sample size. Power analysis for Research
question 5 for a multiple linear regression with four predictors was conducted in G* Power 3.1 to
determine a sufficient sample size using an alpha of 0.05, a power of .90, and a medium effect
size .15; the desired sample for this study is 108.
Procedures
This section describes how the data was collected. After obtaining permission from the
Institutional Review Board, procedures to collect data were initiated. The present study
surveyed a sample of counselors in training via Internet-distributed questionnaires. In order to
achieve this, a list of counseling and social work programs from a Southwestern state were
generated by conducting an internet search. Program directors, coordinators, and faculty from the
generated list were contacted through electronic mail and telephone with the purpose of the study
and to solicit participants. Program directors, coordinators and faculty who agreed to distribute
the invitation to their students received another email with the invitation that explained the
purpose, significance of the study and that participation is voluntary and anonymous. Professors
and program directors from five programs agreed to participate in the study by providing the
survey link to their students via email or in class and seven professors allowed a one- time class

45
presentation to help recruit participants. The invitation to participate in the online survey
included a link that directed the participant to a secure online survey created in Qualtrics along
with informed consent and confidentiality information. The survey invitation indicated
questionnaire would take approximately 10 minutes to complete. Initial contact with invitation
for participants was made at the beginning of Fall semester 2017 and three additional follow-up
requests were sent spaced approximately two weeks apart following the initial contact. Other
than having the opportunity to participate in a study and to add to the literature by participating
in the study, no other incentives were offered to participate in the survey. Participants included
students who identified with one of the following disciplines: rehabilitation counseling, social
work, counseling psychology, counseling education, and human services. Qualified participants
were directed to a secure online survey created on Qualtrics and completion of the survey
indicated informed consent. At the conclusion of data collection, all data was exported from
Qualtrics to be analyzed using SPSS 25.
Data Collection
A four part internet-based survey was used to collect essential information for the
purpose of this study. The survey inquired about and gathered demographic information,
counseling training, social justice advocacy competency, and ethical awareness. A demographic
questionnaire was included in the survey to record the participants age, race/ethnicity, disability
status, sexual orientation, ethical awareness and gender. Also, the questionnaire inquired about
the students’ counseling training with questions such as the number of completed
practicum/internship courses, classification (Master level or Doctoral level student), type of
counseling program, the number of social justice advocacy courses and the number of Ethics
courses completed. Additional survey questions inquired about counseling program

46
accreditation status, whether social justice competency has been evaluated, and highest education
level attained. The demographic information was utilized to describe the participants, observe
frequency and used as the independent variables in data analysis. In addition to demographic
data, self- reported social justice advocacy competency and ethical awareness was collected.
The instruments that were used in this study are the Advocacy Competencies Self-Assessment
(ACSA) Survey and the Ethical Leadership Questionnaire.
Instruments
The Advocacy Competencies Self-Assessment (ACSA) Survey is a self-assessment that
measures level competence in six advocacy domains. The instrument was created specifically to
measure social justice advocacy competency for counselors therefore the questionnaire was not
modified. The ACSA has a total of 30 items that instructs the participant to rate themselves on
six domains; client/student empowerment, community collaboration, public information,
client/student advocacy, systems advocacy, and social/political advocacy on a three-point Likert
scale ranging from Almost Never (0), Sometimes, (2), and Almost always (4). The range of
scores for each of the six advocacy domains is from 0 to 20. Adding the total score for the six
advocacy domains determines participants’ overall advocacy rating scale. The total range of
scores possible is from 0 to 120. Scores of 69 and below indicate that participants may need
further training in a particular advocacy domain. Scores ranging from 70 to 99 indicate that
participants have demonstrated competence with certain advocacy domains but may need to
further develop competence in other advocacy areas. Scores ranging from 100 to 120 indicate a
high level of competence in each of the six advocacy domains. The total scale score and the
range of scores for each of the six domains will be used for this study. Knowing where a student
is lacking in a particular advocacy domain can assist counselor educators create appropriate and

47
meaningful curricula and help students become aware of their strengths and weaknesses. An
example of a question used in the ACSA survey includes “I distinguish when problems need to
be resolved through social advocacy.” The ACSA was found to have adequate internal
consistency, a Cronbach’s alpha coefficient of .93 and mixed results in terms of its construct
validity (Bvunzawabaya, 2012). Feldwisch and Whiston (2015) examined social justice
advocacy competencies of school counselors and reported Cronbach’s alpha coefficient for the
ACSA to be .91. The ACSA is a good fit for this study because the survey items are influenced
by the American Counseling Associations Advocacy competencies. Permission from the authors
of the ACSA was granted electronically through an email.
The Ethical Leadership Questionnaire (ELQ) is a 23-item questionnaire with three
subscales measuring ethical leadership; the items are designed to elicit a reflection on one’s own
professional conduct when faced with real ethical dilemmas at work (Langlois, Lapointe, Valois,
& de Leeuw, 2014). It is designed to measure the presence of ethical leadership based on the
three ethical dimensions: justice, care, and critique. It is intended to assist individuals gain
awareness of their ethical profile by identifying their acquired and emerging ethical
competencies; including identification of ethical sensitivity, an important factor for ethical
decision making. Langlois and Lapointe (2010) emphasize that their goal was to develop an
instrument that is able to identify the presence of emergent or confirmed ethical competency
among leaders and to support their optimal development through professional training. The ELQ
measures the presence of Ethic of critique (seven items), Ethic of justice (six items), and Ethic of
care (ten items) based on Starratt’s (1991) Ethical Leadership Model. Respondents are asked to
rate each statement on a six-point Likert scale with response options ranging from 1 (Never) to 6
(Always). The total range of scores possible is from 0 to 138. Higher scores are interpreted to

48
reflect a greater level of ethical competencies. Items 1, 2,5, 8, 9, 17, 18, 19, 20, 21 measure the
Ethic of Care, items 3, 6, 7, 10, 11, 16, 23 measure Ethic of Critique, and items 4, 12, 13, 14, 15,
22 measure the Ethic of Justice. The ELQ went through seven validation processes to determine
validity of instrument. Item response theory (IRT) was used to verify the reliability and the
psychometrics properties of the ELQ. A study reports discriminant validity for the ELQ as the
inter-factor correlations range from .75 to .81 and factor loadings were satisfactory with the
exception of three loadings that were less than .3 (Langlois & Houme, 2008). The instrument is
reported to have good internal consistency, Cronbach’s alpha coefficient, .80 (Langlois et al.,
2014). Items of the ELQ were found to not be gender biased so the ELQ will provide more
reliable results in diverse research settings. Permission to use the ELQ was granted from the
authors electronically through an email.
Data Analysis Procedures
Data analysis was done using IBM SPSS Statistics Version 25 (IBM Corp, 2017).
Descriptive statistics and inferential statistics were carried out on all independent measures and
dependent measure. Data analysis procedures are described below:
Descriptive statistics
Descriptive statistics are useful for describing general information and characteristics of
the participants in a study and is typically used to summarize the collection of data. It is also
applied in support of study sample to be a representation of the sampled population. For the
purposes of this study, the following descriptive statistics were used: frequency, mean,
percentages, rank order, and standard deviations to analyze the demographic data, rank order of
SJA domains, social justice advocacy competency and ethical awareness. Demographic/social
characteristics (gender, age, race/ethnicity, disability status, ethical awareness) and counseling

49
training (classification, type of counseling program, accreditation status, advocacy training, and
practicum/internship courses) data of counselor trainee was gathered. This information was
utilized to describe the make-up of the sample and to observe frequency. Also, this method
helped describe the score distribution for social justice advocacy competency and ethical
awareness of the counselor trainees. More specifically, descriptive statistics was employed to
answer the following research questions: RQ1. How do counselor trainees rate their level of
competency in social justice advocacy? RQ1.1, How does counselor trainee’s rank order the
importance of each social justice advocacy competency domain? RQ2, How do counselor
trainees rate their level of ethical awareness?
Inferential Statistics
This study applied the Pearson product-moment correlation, independent sample t-test,
stepwise multiple regression to determine the relationship between variables, if significant
differences existed between groups, and examine if variables were predictors of social justice
advocacy competency.
Pearson Product -Moment Correlation
A Pearson product-moment correlation coefficient measures the strength of a linear
association between two variables. The Pearson correlation cannot determine a cause-and-effect
relationship and only will establish the strength of linear association between two variables. A
Pearson correlation coefficient, r, value of zero (0) suggests that there is no association between
the two variables.
A Pearson correlation coefficient was used to answer RQ3. What is the relationship
between level of competency in social justice advocacy and level of ethical awareness of
counselor trainees? A Pearson Correlation was conducted to determine the strength and

50
direction of relationship that exists between social justice advocacy competency and ethical
awareness. A correlational analysis was employed to answer Research question 3a. Is there a
significant relationship between each social justice advocacy competency domain and ethical
awareness of counselors in training? A Pearson correlation was performed to determine the
strength and direction of relationship that exists between each social justice advocacy
competency domain and ethical awareness.
Independent Sample T-Test
The inferential statistical test determines whether there is a statistically significant
difference between the means in two unrelated groups in terms of the dependent variable. The
assumptions of normal distribution and homogeneity of variance must be met to run the test.
The independent t-test is regarded as a robust test with respect to the assumption of normality.
The Levene’s Test of Equality of Variance was run and the significance (p) value was greater
than 0.05 so the group variances can be treated as equal. A series of t-tests were used to
determine if social justice advocacy competency scores were different between classification
group means, social justice advocacy course status group means, licensure status group means,
gender group means, sexual orientation group means, Ethics course status group means,
disability status group means, Ethnicity status group means and whether social justice advocacy
competency had been assessed group means.
Multiple Linear Regression
A standard multiple regression is used to determine the predictive relationship between a
dependent variable and two or more independent variables. A multiple regression aims to learn
the overall fit of the model and the input of each of the predictors to the total variance explained.
Cohen suggests f 2 value of .35 represents a large effect size. One recommendation is that you

51
have at least five observations for each variable to run a multiple linear regression. For this
study, a power analysis using G* power was used to determine appropriate sample size.
A stepwise multiple linear regression analysis was used to answer RQ4. A stepwise
multiple regression was conducted to examine if demographic variables (independent, predictor
variables) age, race, gender, sexual orientation, ethical awareness, and disability status can
predict social justice advocacy competency (dependent, criterion variable).
Stepwise regression is a semi-automated process of building a model by successively
adding or removing variables based solely on the t-statistics of their estimated coefficeints.
Outliers can have a large impact on the stepping procedures, so it is recommended that they are
removed before applying method to data. Power analysis for a multiple regression with six
predictors was conducted in G* Power 3.1 to determine a sufficient sample size using an alpha of
0.05, a power of .90, and a medium effect size .15; the desired sample is 123. A stepwise
multiple regression was employed to answer Research question 5. A step wise multiple
regression was used to explore if counselor training (independent variables) such as counseling
program, classification, internship experience, and social justice advocacy course can predict
social justice advocacy (dependent variable). Power analysis for a multiple regression with four
predictors was conducted in G* Power 3.1 to determine a sufficient sample size using an alpha of
0.05, a power of .90, and a medium effect size .15; the desired sample is 108.
The assumptions to be able to run a multiple regression analysis were examined and met.
After removing four possible outliers, the Shapiro-Wilk test and the measures of skewness and
kurtosis demonstrated data is normally distributed. The Shapiro-Wilk p value was above .05 and
z-values for skewness and kurtosis were between -1.96 to +1.96. If the p value of the Shapiro-
Wilk test is below 0.05, the data significantly deviate from a normal distribution. The dependent

52
variable is a continuous variable and the independent variables are both categorical and
continuous variables. Also, analyses were conducted to confirm the assumptions for
multicollinearity, linearity, homoscedasticity, and independence of residual were met.
According to collinearity diagnostics on SPSS, multicollinearity was not found among the
independent variables. The correlation coefficients for each pair of independent variables were
.415 or less; correlations of .8 or higher suggest variables are highly related and indicate
multicollinearity (Huck, 2008). Collinearity statistics was used to measure the relationship
between multiple independent variables. The tolerance values and the variance inflation factor
(VIF) values confirmed assumptions were met to run a multiple regression analysis statistic. VIF
scores were close to 1 and tolerance values were above .75.
Research Design
This is a non-experimental, descriptive design survey that examined the social justice
advocacy competency of rehabilitation counselor trainees. The study employed descriptive
statistics, independent sample t-test, correlation analysis, and stepwise multiple linear regression
analysis to answer the research questions. This study examined a total of ten independent
variables: age, gender, race, sexual orientation, classification, counselor program, internship
experience, social justice advocacy course, ethical awareness. The dependent variable that was
used for this study is social justice advocacy competency. All analyses were conducted using the
latest edition of IBM Statistical Package for the Social Sciences (SPSS) version 25.
Preliminary analysis
Prior to conducting statistical analysis, normality of data was examined in addition to
assumptions to determine if the multiple linear regression analysis statistical test and independent
sample t test would be appropriate. After reviewing scatterplots for ACSA and ELQ scores, five

53
cases appeared to be possible outliers and were removed to achieve normal distribution of data.
The Shapiro-Wilk p value was above .05 and z-values for skewness and kurtosis were between -
1.96 to +1.96. If the p value of the Shapiro-Wilk test is below 0.05, the data significantly deviate
from a normal distribution (Kirk, 2008). Also, analyses were conducted to confirm the
assumptions for multicollinearity, linearity, homoscedasticity, and independence of residual were
met. According to collinearity diagnostics on SPSS, multicollinearity was not found among the
independent variables. Multicollinearity is described as moderate to high intercorrelations among
the predictor variables which limits the size of R (Stevens, 1996). Additionally, data
distributions were observed with a Q-Q plot and a Box plot. The box plot represents the
distribution of scores and can be used to assess the symmetry of a distribution (Duncan &
Howitt, 2004). Figure 3 is a Q-Q plot and Figure 4 is a Box plot that demonstrates the
distribution of scores for the ACSA based on the participants’ responses. All assumptions were
met, and therefore statistical analysis to perform a stepwise multiple linear regression analysis,
Pearson Product correlation analysis, and independent sample t test were performed.
54
Figure 3: Normal Q-Q Plot of ACSA Scores
55
Figure 4: Box Plot for ACSA Scores
Missing data was addressed to protect the validity of research findings. Cohen and
Cohen (1993) suggested that when up to 10% of cases have missing data on a particular variable,
it is not extensive, therefore; the variable should be kept. For cases that had missing responses to
fewer than 10% of the items, a replacement by means method was administered to allow the
computation of total scores for the measure. After this process, sample consisted of one hundred
thirty seven participants. However, in reviewing sample data and scatter plots for ACSA and
ELQ scores, five possible outliers were removed in order to meet the assumptions and run a
multiple linear regression analysis and independent sample t-test. Therefore, the final sample

56
was one hundred and thirty two (N = 132) participants. The scores were used in the multiple
linear regression analysis, independent sample t-test, and a Pearson correlation analysis and to
meet normal distribution assumption, the possible outliers were removed.
A series of point biserial correlation analysis were conducted on SPSS version 25 to
examine the relationship between independent variables (counseling training demographics) with
the Advocacy Competencies Self-Assessment (ACSA) Survey scores. The point biserial
correlation coefficient is a correlation coefficient used when one variable is dichotomous and the
other is continuous. The analysis was run to determine the relationship between ACSA scores
and the variables (licensure status, Ethics course status, competency status, and accreditation
status). There was a small positive correlation between ACSA scores and licensure status (yes
status), which was statistically significant; r(132) = .18, p < .036. There was a small positive
correlation between ACSA scores and Ethics course (yes status), which was not statistically
significant; p > .262. There was a small positive correlation between ACSA scores and whether
social justice competency was assessed (yes status), which was statistically significant; r(132) =
.22, p < .010. There was a small negative correlation between ACSA scores and accreditation
(CACREP status), which was not statistically significant; p > .769. Table 1 provides the point
biserial correlations between variables and ACSA scores.

57
Table 1
Point Biserial Correlations Between Variables and ACSA Scores
Variables
Pearson
p value (N = 132)
Classification (Doctoral)
.177*
.042
Licensure status (yes)
.183*
.036
Ethics course (yes)
.098
.262
SJA competency assessed (yes)
.224**
.010
Accreditation status (CACREP)
-.026
.769
*p < .05, two-tailed. **p < .01, two-tailed.
ACSA = Advocacy Competencies Self-Assessment Survey
CACREP = The Council for Accreditation of Counseling & Related Educational Programs

58
CHAPTER V
RESULTS
Descriptive Statistics
Participants
One hundred and seventy one people opened the survey link, 168 gave consent and
completed some part of the questionnaire; three did not give consent and did not complete
survey. Missing data was addressed to avoid having invalid data. Cohen and Cohen (1993)
suggested that when up to 10% of cases have missing data on a particular variable, it is not
extensive, therefore; the variable should be kept. For cases that had missing responses to fewer
than 10% of the items, a replacement by means method was administered to allow the
computation of total scores for the measure. After this process, sample consisted of 137
participants. However, in reviewing sample data and scatter plots for ACSA and ELQ scores,
five possible outliers were removed in order to meet the assumptions and run a multiple linear
regression analysis and independent sample t-test. Therefore, the final sample was 132
participants. The scores were used in the multiple linear regression analysis, independent sample
t-test, and a Pearson correlation analysis and to meet normal distribution assumption, the
possible outliers were removed. The survey was organized to include the two questionnaires at
the beginning of the survey followed by demographic information and counseling training
information questions at the end. This was done to ensure that participants would complete the
questionnaires since a purpose of this study was to gather data about social justice advocacy

59
competency and ethical awareness of counselor trainees. Participant responses were recorded
and it was noted if a question did not have a response. Table 2 contains an overview and
frequencies of key demographic variables such as gender, age, ethnicity, disability status, and
sexual orientation.
Table 2
Descriptive Statistics: Demographic Characteristics of Survey Sample
Variable
Frequency
Percent
Valid percent
Gender (n = 127)
Female
101
76.5
76.5
Male
25
18.9
19.7
Other
1
.8
.8
No response
5
3.8
3.8
Mean age (n = 124)
32
__
__
Ethnicity (n = 126)
Hispanic/Latino (non-White)
77
58.3
61.1
White (non-Hispanic/Latino)
31
23.5
24.6
Black/African American
9
6.8
7.1
Asian
3
2.3
2.4
American Indian or Alaska Native
0
0
0
Multiracial
5
4.1
4.2
Native Hawaiian or Pacific Islander
0
0
0
Other
1
.8
.8
No response
6
4.5
4.6

60
Disability Status (n = 126)
Psychological
10
7.6
7.9
Physical
5
3.8
4.0
Multiple
7
5.3
5.6
Cognitive
3
2.3
2.4
Developmental
1
.8
.8
No Disability
100
75.8
79.4
No Response
6
4.5
4.6
Sexual Orientation (n = 123)
Heterosexual
112
84.8
91.1
Lesbian
4
3.0
3.3
Bisexual
3
2.3
2.4
Gay
2
1.5
1.6
Other
2
1.5
1.6
No response
9
6.8
6.8
Table 3 provides an overview and frequencies of key counseling training variables regarding
classification, counseling program, accreditation status, licensure/certification status, completed
practicum/internship, social justice advocacy course, Ethics course, and whether social justice
advocacy competency has been assessed.

61
Table 3
Descriptive Statistics: Counseling Training Characteristics of Survey Sample
Variable
Frequency
Percent
Valid Percent
Classification (n = 126)
Master’s level
102
77.3
77.3
Doctoral level
24
4.5
4.5
No response
6
4.5
4.5
Counseling program (n = 127)
Rehabilitation Counseling
77
58.3
60.6
Social Work
26
19.7
20.5
Counseling (Education)
14
10.6
11.0
Counseling (Psychology)
3
2.3
2.4
Human Services
1
.8
.8
Other
6
4.5
4.7
No Response
5
3.8
3.8
Accreditation status (n = 127)
CACREP
68
51.5
53.5
CORE
19
14.4
15.0
CSWE
18
13.6
14.2
None
21
15.9
16.5
Other
1
.8
.8
No Response
5
3.8
3.8
Licensure/certification (n = 127)

62
Yes
28
21.2
22.0
No
99
75.0
78.0
No Response
5
3.8
3.8
Internship/Practicum (n = 122)
Yes
81
64.1
66.4
No
41
31.1
33.6
No Response
10
7.6
7.6
SJA course (n = 127)
Yes
22
16.7
17.3
No
105
79.5
82.7
No Response
5
3.8
3.8
SJA assessed (n = 124)
Yes
23
17.4
18.5
No
101
76.5
81.5
No Response
8
6.1
6.1
Ethics Course (n = 127)
Yes
55
41.7
43.3
No
72
54.5
56.7
No Response
5
3.8
3.8
Note. SJA = Social Justice Advocacy
A convenience sample of counselor trainees who are in a master’s-level or doctoral level
rehabilitation counseling program or related counseling program was utilized for this study. In
total, 132 counselors in training completed an online survey, of whom 101 were female, 25 were

63
male, 1 identified as other (dissociative identity disorder); 5 did not report. More than half of the
participants (n = 77) self-identified their race/ethnicity as Hispanic/Latino non-White. Other
race/ethnicity reports included White non-Hispanic/Latino (n = 31), Black or African American
(n = 9), Asian (n = 3), Multiracial (n = 6), Other (n = 2); 6 did not report. Participants’ age
ranged from 20 to 65 years (M= 31.7, SD= 9.0). With regard to sexual orientation, 112
participants self- identified as heterosexual, 4 as lesbian, 3 as bisexual, 2 as gay, and 2 as other
(pansexual); 9 did not report. A majority of the participants (n = 100) reported disability status
as no disability. Other disability statuses that were reported included psychological disability (n
= 10), physical disability (n = 5), other/multiple disability (n = 7), cognitive disability (n = 3),
developmental disability (n = 1); 6 did not report. Seventy-seven participants were enrolled in
rehabilitation counseling program, social work program (n = 26), counseling education program
(n = 14), other counseling program (n = 6), counseling psychology program (n = 3), human
services program (n = 1); 5 did not report. A majority of participants were enrolled in a
CACREP counseling accredited program (n = 68), CORE counseling accredited program (n =
19), CSWE social work accredited program (n = 18), non- accredited program (n = 21), other (n
= 1); 5 did not report. One-hundred and two participants self-reported their student classification
as a master level student and 24 as a doctoral level student; 6 did not report. More than half of
participants (n = 81) self-reported they completed a practicum/internship course and 41 did not
complete a practicum/internship course; 10 did not report. With regard to licensure/certification
status, 28 of the participants reported they hold a license/certification, 99 do not, and 5 did not
report. One-hundred and five participants self-reported they have not completed a stand- alone
social justice advocacy course, 22 did complete a course, and 5 did not report. A majority of the
participants (n = 101) self -reported their social justice advocacy competency had not been

64
assessed or evaluated; 23 were assessed at work, by a supervisor, or self; 8 did not report.
Eighty-three participants reported a Bachelor’s degree was the highest degree completed, (n =
38) reported Master’s degree, (n = 2) reported Doctoral degree, (n = 8) reported other, and 1 did
not report. Participants were asked to rank order the Social Justice Advocacy domains from the
most important to the least important with 1 meaning the most important and 6 meaning the least
important, 1 = (Most important) to 6 = (Least important). The client empowerment domain was
selected as most important 67 times, community collaboration domain was selected as most
important 6 times, public information domain was selected as most important 9 times, client
advocacy domain was selected as most important 17 times, systems advocacy domain was
selected as most important 6 times, and social/political advocacy domain was selected as most
important 15 times. Table 5 contains the most important rank frequency for social justice
advocacy domains.
RQ1
Descriptive statistics was run on SPSS version 25 to examine advocacy competency
score. The mean score and standard deviation was (M = 82.43, SD = 16.647). Figure 3 is a
histogram that indicates the mean and standard deviation for advocacy competency based on the
participants’ responses. Scores ranging from 70 to 99 indicate that participants have
demonstrated competence with certain advocacy domains but may need to further develop
competence in other advocacy areas. Scores ranging from 100 to 120 indicate a high level of
competence in each of the six advocacy domains. The range of scores for each of the six
advocacy domains is from 0 to 20. The client advocacy domain had the highest mean score,
followed by client empowerment then communication collaboration. The mean score for client
advocacy was (M = 16.21), client empowerment (M = 15.35), communication collaboration (M =
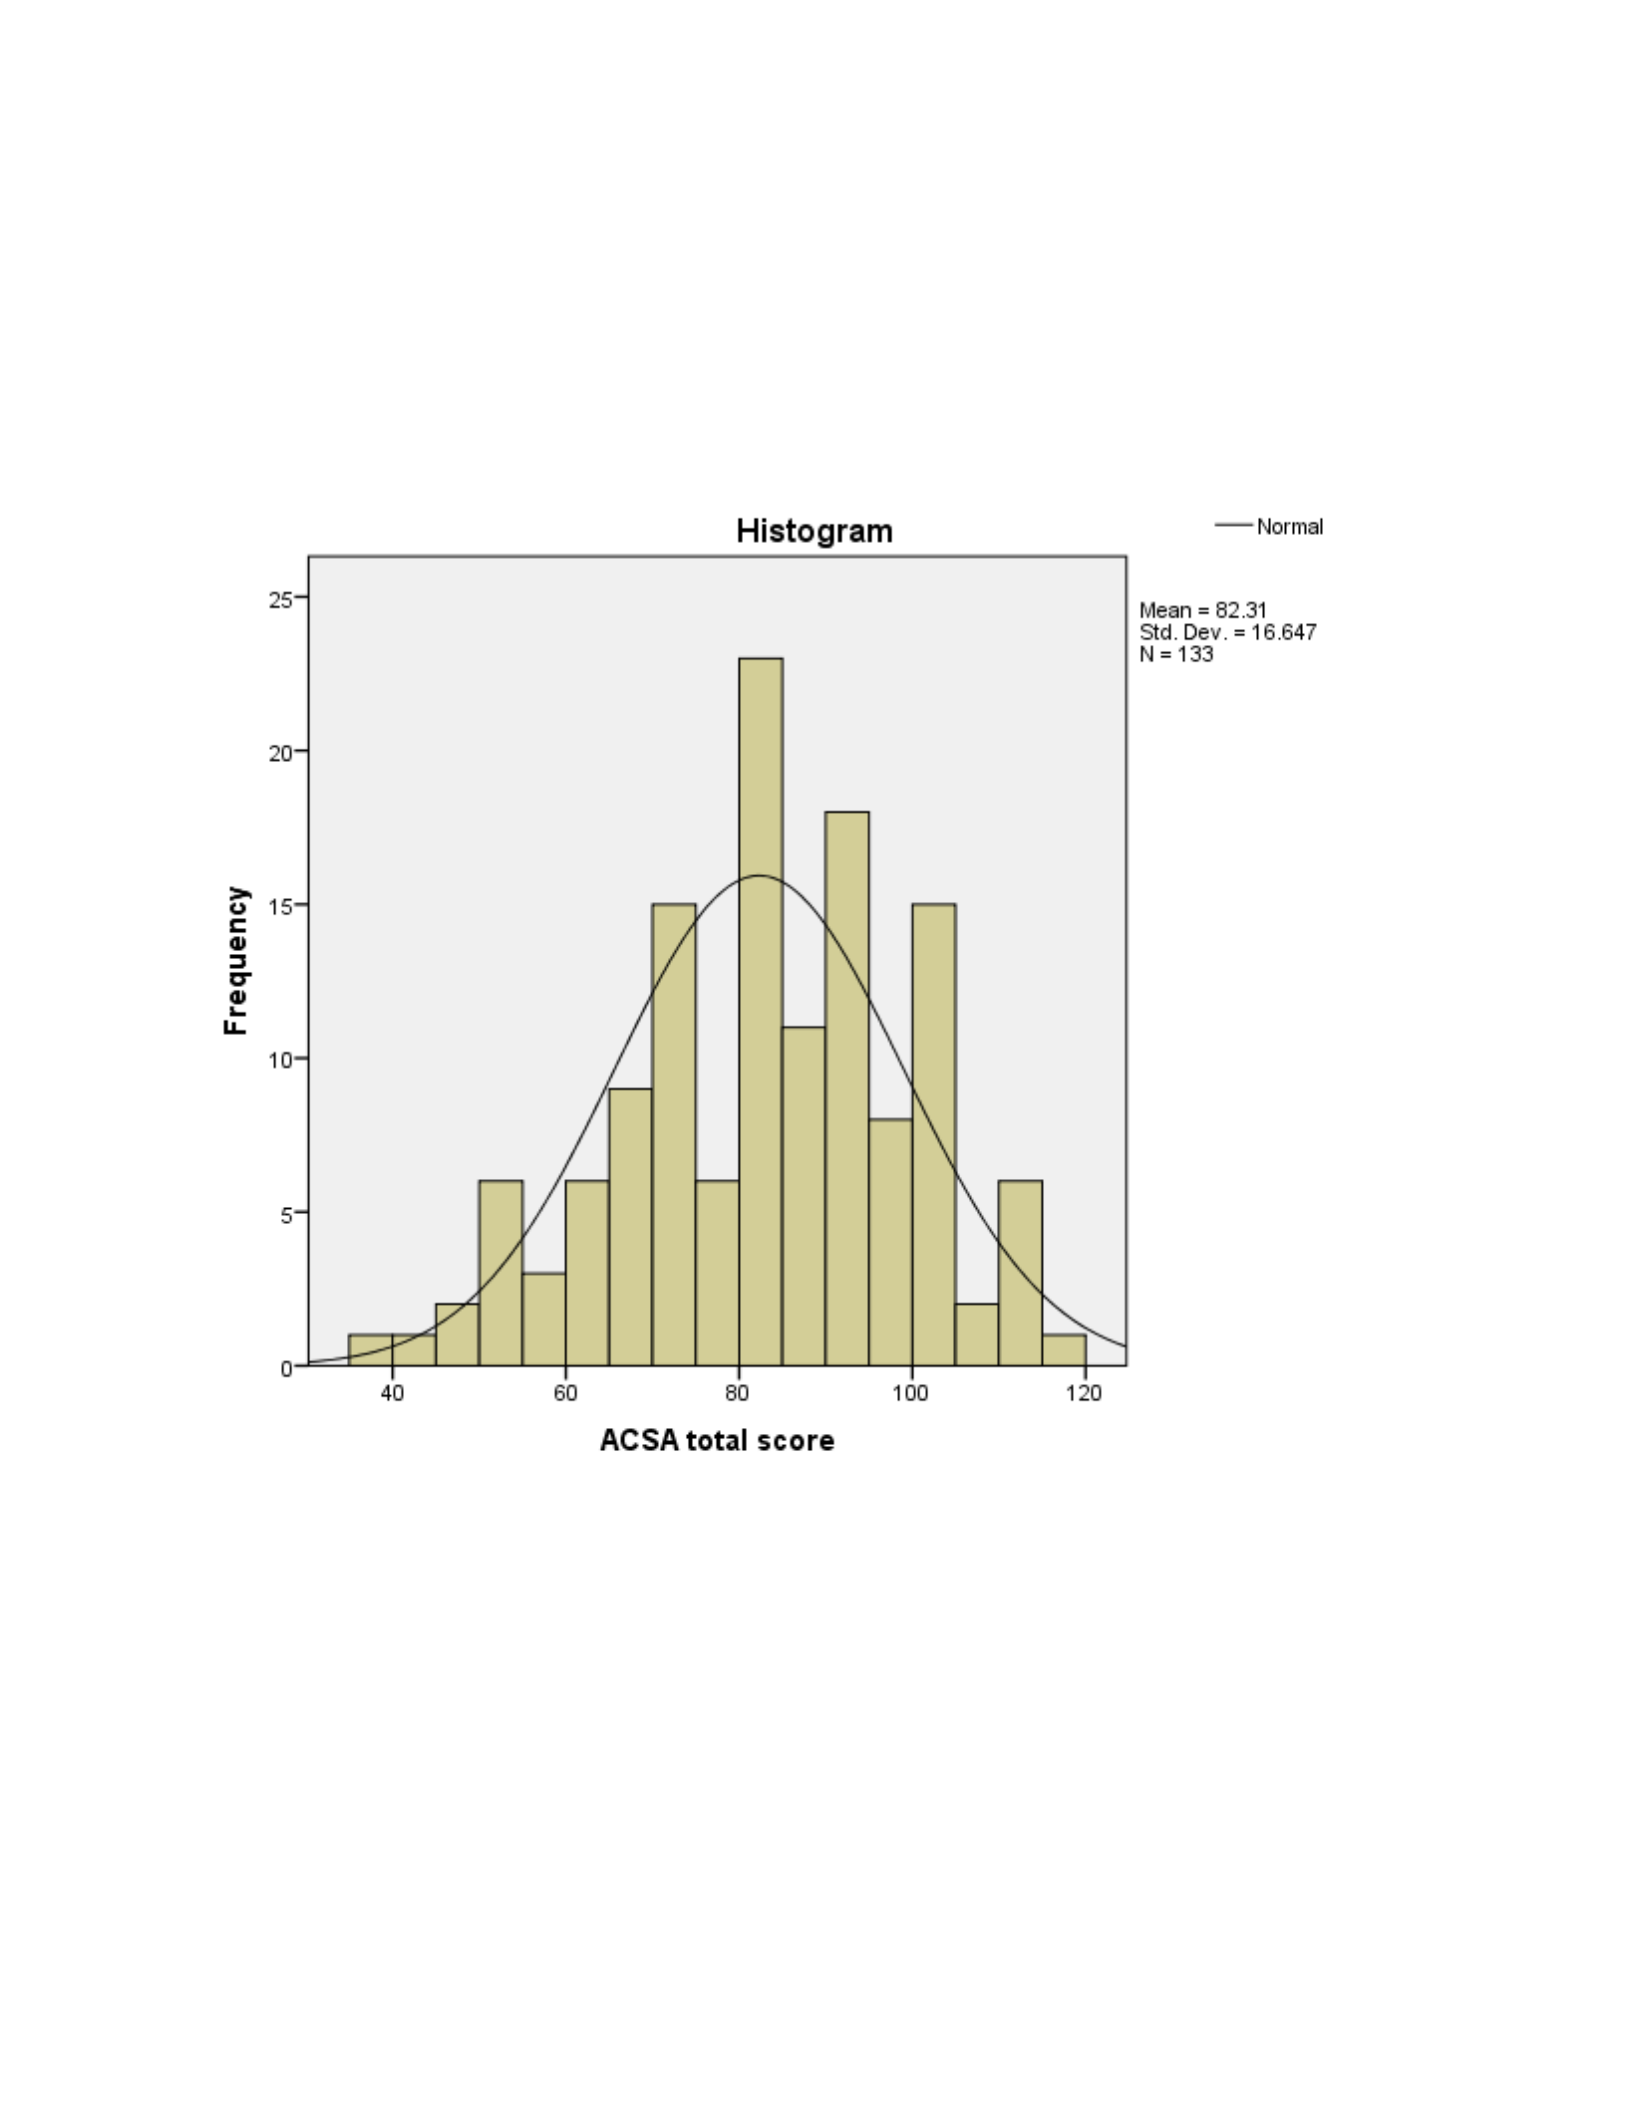
65
14.53), systems advocacy (M = 12.85), public information (M = 12.05), and social political
advocacy (M = 11.44). Table 4 contains the mean and standard deviation of each social justice
advocacy competency domain. Figure 5 demonstrates a histogram with the mean and standard
deviation of social justice advocacy competencies scores for the sample.
Figure 5: Histogram of M and SD for ACSA Scores

66
Table 4
Mean and Standard Deviation of Advocacy Competencies Domains
SJA Domain
Mean
Standard Deviation
Client Advocacy
16.21
2.95
Client Empowerment
15.35
3.07
Community Collaboration
14.53
3.39
Systems Advocacy
12.85
3.95
Public Information
12.05
3.81
Social/Political Advocacy
11.44
4.49
Note. Range for competencies domains, 0-20
RQ1.1
Participants were asked to rank order the Social Justice Advocacy domains from the most
important to the least important with one meaning the most important and six the least important,
1 = (Most important) to 6 = (Least important). The frequency and percentage of most important
and least important rank was recorded for each domain. The client empowerment domain was
selected as most important 67 times, 51% and as least important 15% , community collaboration
was selected as most important 6 times, 4.5% and as least important 2.3%, public information
was selected as most important 9 times, 6.8% and as least important 23.5%, client advocacy was
selected as most important 17 times, 12.9% and as least important 1.5%, systems advocacy was
selected as most important 6 times, 4.5% and as least important 14.4%, and social/political
advocacy was selected as most important 15 times, 11.4% and as least important 30.3%. Table 5
demonstrates the frequency for each domain, frequencies for most important and least important
are reported.

67
Table 5
Most Important Rank Frequencies for Advocacy Domains
SJA Domain Frequency
Most Important Least Important
Client Empowerment 51.0%
67 22
Client Advocacy 12.9%
17 2
Social Political Advocacy 11.4%
15 41
Public Information 6.8%
9 32
Systems Advocacy 4.5%
6 20
Community Collaboration 4.5%
6 3
Note. Most Important and Least Important Reflect the Number of Times Domain Was Selected
RQ2
Descriptive statistics was performed on SPSS version 25 to examine ethical awareness
score. The mean score and standard deviation were (M = 113.03, SD = 13.01). The total range
of scores possible is from 0 to 138. The mean score for the Ethic of Care was (M = 52.13), Ethic
of Critique (M = 31.46), and Ethic of Justice (M = 29.45).
Inferential Statistics
RQ3
A Pearson product-moment correlation was run on SPSS version 25 to determine the
relationship between Social Justice Advocacy competency and Ethical awareness in 132
counselors in training. There was a small positive correlation between Social Justice Advocacy
Competency and Ethical awareness, which was statistically significant; r(132) = .23, p < .008.
Table 6 reports the correlation matrix for Social Justice Advocacy scores and Ethical awareness
scores. Figure 6 demonstrate a scatterplot that indicates as ethical awareness scores increase,

68
social justice advocacy competency scores increase. Consequently, it suggests a positively-
sloped regression line.
Table 6
Pearson Correlation between ACSA and ELQ scores (N = 132)
ACSA
ELQ
ACSA
__
.23*
ELQ
__
__
Note. * p < .01, two-tailed.
ACSA = Social Justice Advocacy competency
ELQ = Ethical Leadership Questionnaire
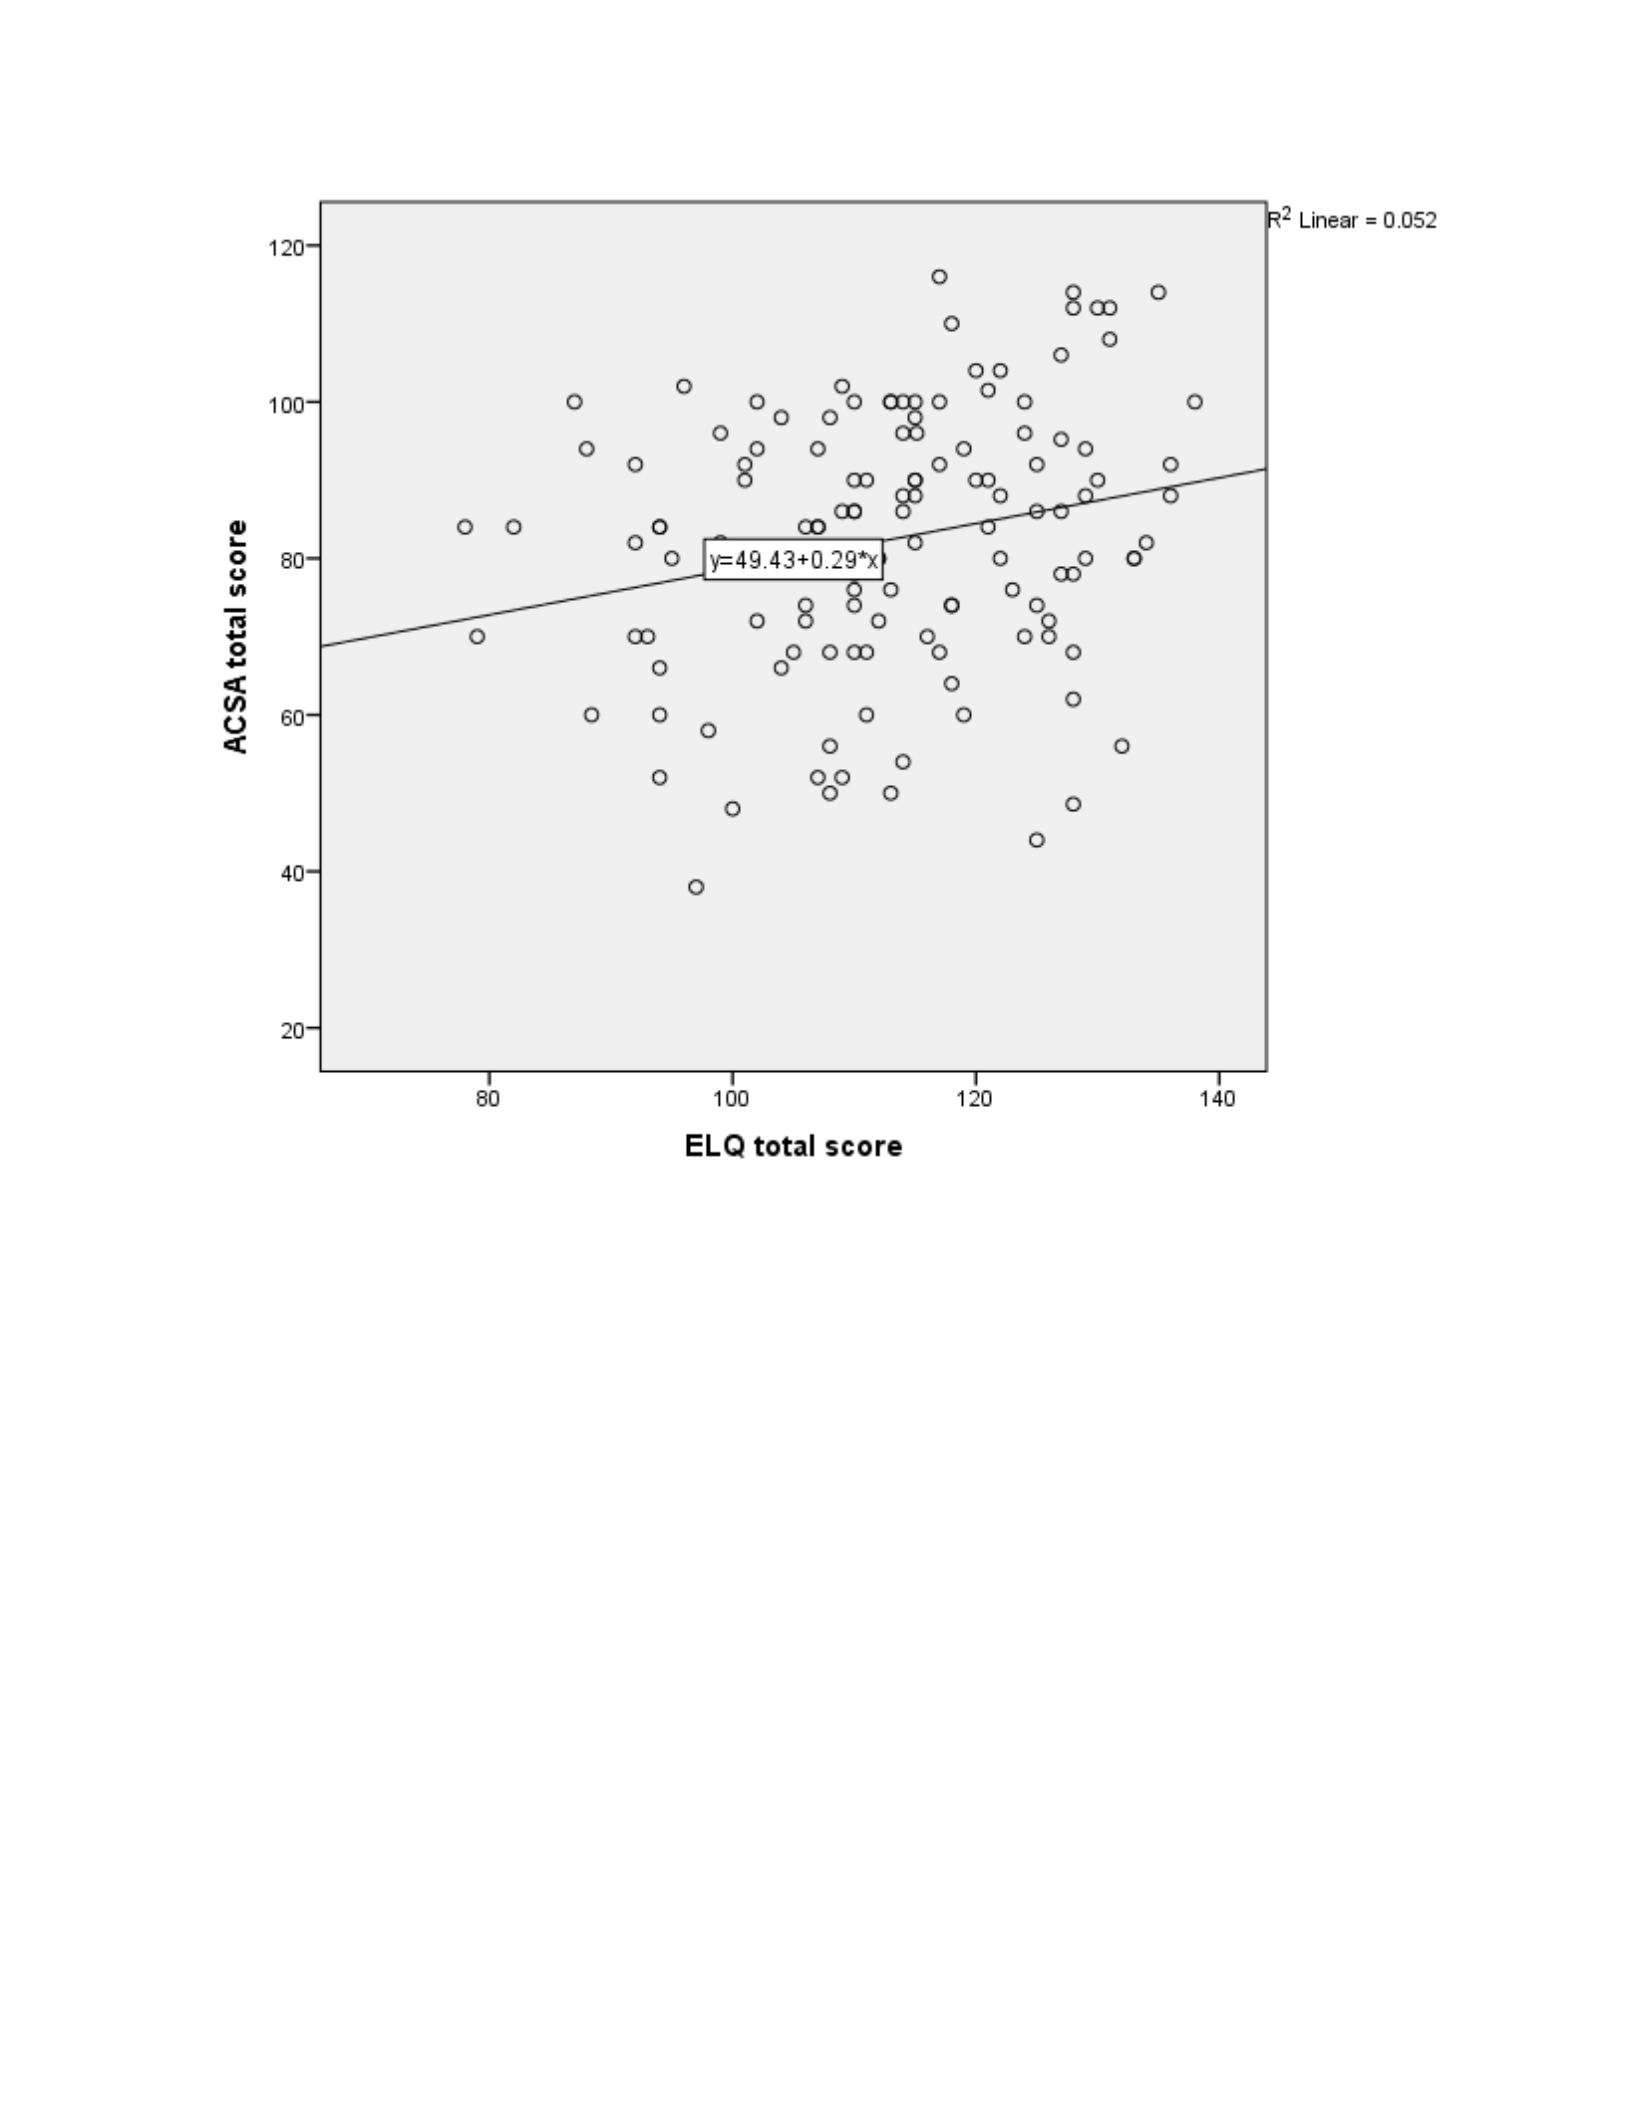
69
Figure 6: Scatterplot of the Relationship Between ELQ Scores and ACSA Scores
RQ3.1
A Pearson product moment correlation was run on SPSS version 21 to assess the
relationship between ethical awareness and SJA subscales (domains) in 132 counselor trainees.
There was a small positive correlation between Ethical awareness and client empowerment
domain, which was statistically significant; r(132) = .20, p < .020. There was a small correlation
between ethical awareness and community collaboration domain, which was not statistically
significant; p > .130. There was a small positive correlation between ethical awareness and
client advocacy domain, which was statistically significant; r(132) = .21, p < .015. There was a
small correlation between ethical awareness and systems advocacy domain, which was

70
statistically significant; r(132) = .20, p < .023. There was a small correlation between ethical
awareness and social political advocacy domain, which was not statistically significant p > .114.
There was a small correlation between ethical awareness and Public Information domain, which
was statistically significant r(132) = .19, p < .033. Table 7 demonstrates the bivariate
correlations for advocacy competencies domains and ELQ scores.
Table 7
Bivariate Correlations for Advocacy Competencies Domains and ELQ Scores
Domain 1 2 3 4 5 6 7
1. CE __
2. CA .514** __
3. SPA .341 ** .473** __
4. PI .230** .429** .645** __
5. CC .471** .471** .681** .547** __
6. SA .342** .512** .583** .555** .621** __
7. ELQ .202* .211* .138 .186* .132 .198* __
Note. N = 132 *p < .05, two- tailed. **p < .01, two-tailed.
RQ4
A multiple regression analysis was conducted to examine the relationship between social
justice advocacy competency and various potential predictors (ethnicity/race, sexual orientation,
age, disability status, ethical awareness, and gender. Given that the majority of the participants
in this study self-identified as Hispanic/Latino non-White (n = 77), race was recoded into a
dichotomous variable: Hispanic/Latino non White and White non-Hispanic/Latino. The same

71
procedure was applied to the other demographic variables; sexual orientation status, was recoded
as Heterosexual and non-Heterosexual, and disability status was recoded to no disability and
disability. Results of the standard multiple regression analysis indicated that there was not a
significant effect between ethnicity, age, gender, sexual orientation, disability status and ethical
awareness. Each of the predictor was dummy coded and entered into the regression model. The
regression is not significant F(6,117) = 1.513, p < .180, the adjusted R2 is .024 percent;
indicating that these variables explained 2.4 percent of the variance in the total ACSA score.
The individual predictors were examined further and indicated that ethical awareness (t = 2.265,
p = .025) was a significant predictor in the model.
A stepwise multiple linear regression analysis was performed to examine the relationship
between social justice advocacy competency and various potential counselor demographic
predictors. The analysis revealed one step, adding one predictor each. Model significantly
predicted social justice advocacy competency. Step 1, indicated variable (ethical awareness)
significantly predicted social justice advocacy competency, Model 1 showed a significant effect,
F(1,122) = 5.475, p < .021 with R2 of .043 and adjusted R2 of .035. This indicates that 3.5
percent of the variation in the advocacy competency score can be explained by the model
containing the variable, ethical awareness. The individual predictors were examined further and
indicated that ethical awareness (t = 2.340, p = .021) was a significant predictor in the model.
However, gender (female), race (Hispanic/Latino non-White), age, sexual orientation
(Heterosexual), and disability status (No disability) were not significant predictors in the model
and were not included in the regression model. Results from the stepwise multiple regression
revealed a significant regression equation for predicting social justice advocacy competencies.
ACSA (y) = 51.601 + .272 (ethical awareness). Participant’s social justice advocacy

72
competency score increased .272 for each point of ethical awareness score. Table 8 contains a
summary of stepwise regression analysis of demographic variables predicting social justice
advocacy competency.
Table 8
Stepwise Multiple Regression Analysis: Variable Predicting SJA Competencies
Variable
B
SE B
β
R2
Adjusted
R2
t
Step 1
Constant
51.601
13.191
ELQ score
.272
.116
.207
.043
.035
2.340
Note. SJA = Social Justice Advocacy ELQ = Ethical Leadership Questionnaire
RQ5
A standard multiple regression analyses was conducted to examine the relationship
between social justice advocacy competency and various potential counselor training predictors.
Results indicated there was a significant effect between completed social justice advocacy
course, completed practicum/internship course, classification, and counseling program. F(4,127)
= 4.658, p < .002. The individual predictors were examined further and demonstrated that
completed social justice advocacy course (t = 2.250, p = .026), completed practicum/internship
course (t = 2.249, p = .026), and student classification-Master’s level (t = -2.271, p = .025) were
significant predictors in the model. However, the variable (counseling program—Rehabilitation
counseling) was not a significant predictor.
A stepwise multiple regression analysis was conducted to examine the relationship
between social justice advocacy competency and various potential counselor training predictors.

73
The analysis revealed three steps, adding one predictor each. Model significantly predicted
social justice advocacy competency. Step 1, indicated variable (completed internship)
significantly predicted social justice advocacy competency, Model 1 indicated a significant
effect, F(1,130) = 7.283, p < .008 with R2 of .053 and adjusted R2 of .046. This reveals that 4.6
percent of the variation in the advocacy competency score can be explained by the model
containing the variable, completed internship. Step 2 denoted variables (completed internship
and classification--Master level) significantly predicted social justice advocacy competency,
F(2, 129) = 6.016, p < .003 with R2 of .085 and adjusted R2 of .071. This refers that seven
percent (7.1 %) of the variation in the advocacy competency score can be explained by the model
containing the variables (complemented internship and student classification—Master level.)
Step 3 indicated variables (completed internship, classification--Master level, and social justice
advocacy course) significantly predicted social justice advocacy competency, F(3, 128) = 5.635,
p < .001 with R2 of .117 and adjusted R2 of .096. This shows that 9.6 percent (9.6%) of the
variation in the advocacy competency score can be explained by the model containing the
variables (completed internship, classification--Master level, and social justice advocacy course).
Further, 90.4 percent of the variation in the social justice advocacy competency score cannot be
explained by the model with the variables (completed internship, classification--Master level,
and social justice advocacy course). Additionally, the variable (counseling program—
Rehabilitation counseling) was not a significant predictor and was not included in the regression
equation model. Results from the stepwise multiple regression revealed a significant regression
equation for predicting social justice advocacy competency. ACSA (y) = 83.337 + 6.284
(completed internship) – 7.900 (Master-level) + 8.071 (Social justice advocacy course). The
participant’s social justice advocacy competency score increased 6.284 points when completed

74
an internship course. The social justice advocacy competency score increased 8.071 points when
completed a social justice advocacy course. A participant’s social justice advocacy competency
score is 7.900 less when student classification is Master level compared to Doctoral level. Table
9 provides a summary of stepwise regression analysis for counseling training variables predicting
social justice advocacy competency.
Table 9
Stepwise Multiple Regression Analysis: Training Predicting SJA Competencies
Variable
B
SE B
β
R2
Adjusted R2
T
Step 1
.053
.046
Constant
77.619
2.277
Internship (Yes)
7.846
2.907
.230
2.699
Step 2
.085
.071
Constant
83.344
3.500
Internship (Yes)
7.484
2.873
.220
2.605
Master’s level
- 7.121
3.339
-.180
-2.133
Step 3
.117
.096
Constant
83.337
3.453
.
Internship (Yes)
6.284
2.890
.184
2.174
Master’s level
-7.900
3.314
-.200
-2.384
SJA course (Yes)
8.071
3.787
.181
2.131
Note. SJA = Social Justice Advocacy

75
Cronbach’s Alpha
The estimate of the internal consistency reliability using Cronbach’s Alpha for the ACSA
scale was examined; this is done to check reliability of the scale. Cronbach’s Alpha value for
this sample was found to be .871; this suggests acceptable reliability. The estimate of the
internal consistency reliability using Cronbach’s Alpha for the ELQ scale was examined; the
value for this sample was found to be .886; this suggests acceptable reliability. Tavakol and
Dennick (2011) indicate that when alpha is too high it implies that some items are redundant as
they may be testing the same item, therefore, a maximum alpha value of .90 has been
recommend.
Further Analysis of Variables
Independent Sample T-Test
A series of independent–sample t-tests were conducted to compare social justice
advocacy competency scores for several variables. There is a significant difference in social
justice advocacy competency scores for classification (Master level, Doctoral), social justice
advocacy course status (yes course, no course), licensure status (yes licensure, no licensure), and
whether social justice advocacy competency has been assessed or evaluated (yes assessed, no
assessed). There is a significant difference between participants who are classified as Master
level (M = 80.70, SD = 17.07) and as Doctoral level (M = 88.67, SD = 13.17); t(124) = - 2.14 , p
< .03. There is a significant difference between participants who completed a social justice
advocacy course (M = 89.73, SD = 17.38) and who did not complete a social justice advocacy
course (M = 81.19, SD =16.05); t(125) = -2.24, p < .03. There is a significant difference between
students who reported yes for licensure status (M = 88.29, SD = 17.18) and those who reported

76
no for licensure status (M = 81.29, SD =15.96); t(125) = -2.02, p < .046. There is a significant
difference between participants who reported yes for social justice advocacy competency has
been assessed (M = 90.52, SD =14.54) and for those who reported no for social justice advocacy
competency has been assessed (M = 80.47, SD = 16.38); t(122) = -2.71, p < .008. There is not a
significant difference in social justice advocacy competency scores for gender (male, female),
sexual orientation (Heterosexual, non-Heterosexual), Ethics course status (yes course, no
course), disability status (yes disability, no disability), and Ethnicity status (Hispanic-non White,
White-non-Hispanic). There is not a significant difference between males (M = 79.36, SD =
15.84) and females (M = 83.36, SD =16.87); p > .29. There were 25 participants who identified
as male and 101 participants who identified as female; six participants did not report gender.
There was not a significant difference between participants who reported sexual orientation
status as Heterosexual (M = 82.26, SD =16.60) and non-Heterosexual (M = 88.55, SD =13.7);
p > .23. There was not a significant difference between participants who reported they
completed an Ethics course (M = 84.6, SD = 16.99) and who did not complete an Ethics course
(M = 81.38, SD = 16.18); p > .32. There was not a significant difference between participants
who reported yes for Disability status (M = 80.00, SD = 18.64) and for participants who reported
no disability (M = 83.31, SD = 16.17); p > .37. There was not a significant difference between
participants who reported as Hispanic non-White (M = 82.00, SD = 17.54) and for those who
reported as White non- Hispanic (M = 83.30, SD = 15.28); p > .67.
Effect Size
The effect size provides a way to measure the magnitude of mean difference. A common
interpretation to refer to effect size is: small (d = .2), medium (d = .5), and large (d = .8);
however, it is noted that these values should not be construed rigidly (Cohen & Cohen, 1993).

77
The following groups indicated a statistical significant difference in group mean so the Cohen’s
d was used to analyze effect size: Classification status t(124) = - 2.14 , p = .03, d = .5; Social
justice course status t(125) = -2.24, p < .03, d = .5; licensure status t(125) = -2.02, p < .046, d =
.4; and assessed social justice competencies t(122) = -2.71, p < .008, d = .6.
Summary
An overview of the statistical results of the study was presented in Chapter IV.
Descriptive statistics was reported to describe demographics and counseling training of sample.
Participants were asked to rank order the six social justice advocacy competency domains from
most important to least important to observe importance frequencies. A Pearson’s correlation
was run to assess the relationship between ethical awareness scores and social justice advocacy
competencies scores. A second Pearson’s correlation was run to observe the relationship
between each competency domain scores and ethical awareness scores. A stepwise multiple
regression was run to examine if demographic variables of counselor trainees predicted social
justice advocacy competencies scores and a second stepwise multiple regression was run to
assess if counseling training variables of counselor trainees predicted social justice advocacy
competencies. Further analysis of variables examined using a series of independent sample t
Tests.

78
CHAPTER V
DISCUSSION
This was an exploratory study and the limited knowledge and lack of empirical research
related to social justice advocacy competency of rehabilitation counselor trainees was the
primary catalyst for this study. The purpose of the study was to examine the competencies of
counselor trainees, more specifically, demographic variables, counselor training, and advocacy
training was explored. This section of the dissertation provides a discussion of the results,
implications, and limitations of the study. This chapter begins with a summary of the findings
followed by the evaluation and conclusions of the research questions, the limitations,
implications for counselor trainees, counseling programs and educators, and future
recommendations.
Summary of Research Questions
The findings for the study are briefly summarized in this section. The mean for social justice
advocacy competency was (M = 82.43) and according to the Advocacy Competencies Self-
Assessment survey, scores ranging from 70 to 99 indicate that participants have demonstrated
competence with certain advocacy domains, but may need to further develop competence in
other advocacy areas. The possible domain range score was from one to twenty and the mean for
each social justice advocacy competency domain were the following: Client Advocacy (M =
16.21), Client Empowerment (M = 15.35), Community Collaboration (M = 14.53), Social
Advocacy (M = 12.85), Public Information (M = 12.05), and

79
Social/Political Advocacy (M = 11.44). The Ethical Leadership Questionnaire instrument was
used to measure ethical awareness and the mean score was (M = 113.03). The total range of
scores for the ELQ instrument is from 1 to 138. Demographic variables such as age, ethnicity,
gender, sexual orientation, and disability status did not predict social justice advocacy
competency for this sample; however, ethical awareness did predict social justice advocacy
competency. Counselor training variables such as completion of a stand-alone advocacy course,
Master-level classification and completion of an internship or practicum course did predict social
justice advocacy competency for this sample; however, counseling program (Rehabilitation
counseling) did not. Furthermore, the variable Master-level classification had an inverse effect
on the social justice advocacy competency score. In regards to relationship of variables, there
was a small positive relationship between ethical awareness and social justice advocacy
competency; as ethical awareness score increased so did the social justice advocacy competency
score; r(132) = .23, p < .008. Participants were asked to rank each advocacy domain from most
to least important, they selected Client Empowerment more frequently as the most important
social justice advocacy domain whereas the domains Community Collaboration and Social
Advocacy were selected more frequently as the least important.
Evaluation and Conclusions
RQ1
The advocacy competency of the participants were examined and measured. Participants self -
reported their social justice advocacy competency and the mean score was (M = 82.43).
According to the Advocacy Competency Self-Assessment survey, scores ranging from 70 to 99
indicate that participants have demonstrated competence with certain advocacy domains, but
may need to further develop competence in other advocacy areas. This finding appears to be

80
typical of counselor trainees and consistent with other studies, for example, Jeon (2014)
examined the competency of Master-level rehabilitation counselor trainees and reported similar
mean scores. Also, Holmberg-Abel (2012) reported finding that counselors demonstrated
competence in some advocacy domains, but not all.
The experience and training reported by this sample appears to have influenced the
advocacy competency score, 77.3% of participants identified as Master-level versus 4.5% who
identified as Doctoral level students. Also, seventy five percent reported they do not hold a
professional license, eighty percent have not completed a stand-alone advocacy course, 77%
reported their competencies have not been evaluated, and 31 % have not completed an
internship/practicum course. The mean score reported for this sample indicated that participants
demonstrate some advocacy skills and knowledge, but need further training to achieve
competencies in certain advocacy domains. An explanation for this finding is that the
participants have not been exposed to a counseling curriculum that incorporates social justice
learning opportunities that facilitate the development of advocacy skills in more than one level or
domain. Previous research has found that counselor trainees report their training and preparation
infrequently integrated the topic of social justice advocacy, specifically, social and systems
advocacy (Holmberg-Abel, 2012; Hudson, Shapiro, Ebiner, Berenberg, & Bacher; 2017
Stackhouse-Powe, 2014). Also, it may be that counselor trainees are more frequently introduced
to traditional counseling perspectives and theories, instead of a social justice theoretical
framework. According to some literature, counseling curriculum that incorporates a theoretical
social justice perspective coupled with practical advocacy models and comprehensive service
learning promotes the advancement of social justice advocacy (Alston et al., 2006; Goodman,
Wilson, Helms, Greenstein, & Medzhitova, 2018; Ratt & Greenleaf, 2018; Toporek &

81
Worthington, 2014). In sum, the findings of the current study suggest counselor trainees have
strengths and needs in social justice advocacy that require to be addressed during their counselor
training and preparation. More specifically, comprehensive counselor training must emphasize
social and political advocacy training during counselor preparation to increase competencies in
social justice advocacy.
Research Question 1.1
Participants were asked to rank order the social justice advocacy competency domains
from the most important to the least important with 1 meaning the most important and 6 meaning
the least important. The client empowerment domain was selected overwhelmingly over the
other domains as most important (51.1%), followed by client advocacy (12.9%), social political
advocacy (11.4%), public information (6.8%), systems advocacy (4.5%), and community
collaboration (4.5%). This finding is consistent with a previous study where counselors
indicated empowerment and self -advocacy was the most important type of advocacy compared
to other types such as systems advocacy. In that study, the counselors also reported that their
advocacy competency, interest, and training had an influence in the level of advocacy they
engaged in (Fickling, 2016). Another study reported similar findings, it found that counselors
ranked client empowerment and client advocacy as “very important” compared to social/political
advocacy which was ranked as “important” (Holmberg-Abel, 2012).
The findings of the current study suggests that counselor confidence, training and
perceived competency explains what level of advocacy a counselor will engage in. For instance,
Homberg-Abel (2012) reported that counselors who ranked client empowerment and client
advocacy as “very important” also reported engaging in higher frequency of activities related to

82
this level of advocacy. Furthermore, they reported they were “very much to extremely” prepared
for advocacy at this level.
An interesting observation of the current study is the notable difference in frequency that
participants ranked client empowerment advocacy as the most important compared to the other
advocacy domains. A possible reason that explains the difference may be related to their
perceived competency with the client empowerment domain compared to the other domains. In
other words, they ranked it the most important since they have more knowledge and experience
with strategies and interventions related to the client empowerment domain. Holmberg-Abel
(2012) found that professional counselors ranked the social justice advocacy domains based on
their confidence and ability to engage in that advocacy domain. Furthermore, that study found
that counselors ranked advocacy domains differently. He reported that counselors ranked client
empowerment and client advocacy as “very important” compared to social/political advocacy
which was ranked as “important.”
Another observation about the rank findings are related to the counseling profession. A
reason for the high frequency may be explained by the counselor trainees’ interest and familiarity
with the strategies, type of engagement and skills associated with client empowerment.
According to the ACA advocacy competencies, competency in client empowerment entails direct
engagement with the client, train clients to become self- advocates, identify strengths and
resources of client among other interventions. The client empowerment domain competencies
are skills that are traditionally associated in helping professions such as counseling, which is
possibly why participants ranked this domain as most important more frequently. The
community collaboration advocacy domain was ranked most important the least frequently.
According to the ACA advocacy competencies, competency in community collaboration entails

83
the ability to engage and collaborate as an ally for the community and local organizations. The
community collaboration domain competencies are skills that are not traditionally associated
with counseling, which is possibly why participants ranked this domain as most important the
least frequently.
For the current study, advocacy competency domain mean scores were highest for client
advocacy (M = 16.21) and client empowerment (M = 15.35), followed by community
collaboration (M = 14.53), then systems advocacy (M = 12.85), and public information (M
=12.05), finally social/political advocacy (M = 11.44). These findings were consistent with a
study by Jeon (2014), who reported counseling trainees’ advocacy competency scores were
higher for the client advocacy domain and client empowerment domain when compared to the
other domains.
It is recommended that counselor trainees and educators expand advocacy training and
preparation to include non- traditional counseling perspectives to improve advocacy in all
domains. Hudson, Shapiro, Ebiner, Berenberg, and Bacher (2017) suggest training programs
that integrate social justice within the classroom climate and within the program’s policies
promote student social justice reflection and are more likely to prepare students to be social
change agents. A study by Holmberg-Abel (2012) also reported that interest, confidence, and
commitment to social justice advocacy increased with social supports and with a social justice
orientation. Thus, it is likely rehabilitation counseling trainees with more social justice advocacy
training may enhance their counseling effectiveness when working with people with disabilities.
RQ2
Ethical awareness of participants was measured and recorded. The ELQ instrument was
used to measure ethical awareness and the mean score was (M = 113.03). The total range of

84
scores for the ELQ instrument is from 1 to 138. This result may be reflective of the participants’
experience and preparation, 55 percent of the participants reported they have not completed a
stand-alone Ethics course at the time of the survey. As previously mentioned, the majority
(77%) of participants identified as Master-level students and most all (75%) reported they do not
hold a professional license. Still the reported mean appears to be average considering the highest
possible scoring range suggesting that although more than half reported they have not completed
a stand- alone Ethics course, participants demonstrate average ethical awareness. Finding
regarding ethical awareness is consistent with another study that examined the ethics education
in master’s rehabilitation counseling programs in the U.S. (Tsai, 2013). The study also found
that students’ self- reported moderate level of confidence and competency in handling ethical
situations based on their training.
One explanation why this sample revealed moderate ethical awareness may be due to
their counseling program accreditation status. The majority of participants reported they were
enrolled in an accredited counseling program (CACREP, 51.5%; CORE, 14.4%; CSWE, 13.6%).
According to accredited counseling programs such as CACREP, Section 2 (F.1.i.) the curriculum
must include ethical standards of professional counseling organizations and credentialing bodies,
and applications of ethical and legal considerations in professional counseling. It is likely that
participants may have been exposed to discussions related to ethics even though most reported
they did not complete a stand-alone Ethics course. Thus, accredited counseling programs that
include ethics in the curriculum and not necessarily a stand-alone course still may influence
counselor achievement in ethical awareness. The ELQ has three subscales which measures
ethical reasoning based on Ethic of care, Ethic of critique, and Ethic of justice. The mean score
for Ethic of care (M = 52.13) was higher compared to the other two subscales, this supports

85
research by Simonis (2009) who reported similar findings. Another study that examined the
impact of ethics education on rehabilitation counseling students found that students demonstrated
their ethical reasoning based on an Individual level ethical orientation (Tsai, 2013). An
Individual level ethical orientation means ethical dilemmas are resolved by considering the rights
and needs of the person. In brief, the ethic of care refers to ethical reasoning based on the value
of caring for others and the value of relationships (Gilligan, 1995). It appears rehabilitation
counseling students’ ethical orientation is influenced by ethics education and training. The Ethic
of care subscale appears to be measuring ethical awareness based on skills and values compatible
with counseling and social justice advocacy. Consequently, the current findings demonstrate
moderate ethical awareness for this sample suggesting ethics education has an influence on
ethical awareness and social justice advocacy competency.
RQ3
The relationship between advocacy competency and ethical awareness was explored. A
small positive, statistically significant correlation between the Ethical Leadership Questionnaire
and the Advocacy Competencies Self-Assessment Survey was observed. Results are consistent
with previous research that indicated ethics knowledge and awareness is critical to achieving
social justice advocacy competency (Cohen, 2004; Stone & Zirkel, 2010).
The finding of the study suggests a relationship between ethical awareness and advocacy
competency. For instance, someone who perceives to have ethical awareness is likely to also
perceive to have social justice advocacy competency. This implies that the participants’
confidence in ethical awareness has an influence on their social justice advocacy competencies;
thus competency in one increases competency in the other. Another explanation for the finding
may be related to the instruments used to measure the two variables. The instrument used to

86
measure ethical awareness has three subscales (ethic of care, ethic of justice, ethic of critique).
This suggests the instruments used to measure ethical awareness and social justice advocacy
have similar, but not identical constructs. According to the literature review, this was the first
study to investigate the relationship between ethical awareness and competencies in social justice
advocacy in relation to counselor trainees; therefore, more research is warranted to provide
comprehensive implications.
RQ3.1
The relationship between each advocacy competency domain and ethical awareness was
measured. A small positive, statistically significant correlation between the Counselor
Empowerment domain of the Advocacy Competencies Self-Assessment and the Ethical
Leadership Questionnaire was observed, this was also true for the Counselor Advocacy domain,
Public Information domain, and the Systems Advocacy domain. This finding suggests that
ethical awareness improves advocacy competency for specific advocacy domains, but not in all
domains. However, a small and positive non- statistically significant relationship between the
Ethical Leadership Questionnaire and Social/Political advocacy domain and the Community
collaboration domain was observed. For this sample, ethical awareness did not significantly
influence advocacy competency in community collaboration and social/political advocacy
domains. It is possible that other factors and not necessarily ethical awareness may have a
bigger influence on advocacy competency for different levels and domains. As one study
pointed out, advocacy training that is extensive and involves a social justice perspective
approach including practical advocacy models have demonstrated to facilitate social justice
advocacy competency in counselor trainees (Goodman et al., 2018). Another possible
explanation for the current finding may be related to ethics education and training. Tsai (2013)

87
examined the influence of ethics education on ethical awareness and found confidence and
competency was related to satisfaction of education. Those who reported moderate satisfaction
also reported moderate ethical awareness in regards to confidence and competence. Thus for the
current study it is possible that the competency mean score was the lowest for the social political
advocacy domain because counselor trainees were not satisfied with their preparation in social
political advocacy. As previous mentioned, there is a lack of current literature that has examined
the relationship between ethical awareness and social justice advocacy competency, thus, these
findings merit further investigation.
RQ4
The influence of personal demographic variables such as gender, ethical awareness, age,
sexual orientation, ethnicity, and disability status on social justice advocacy competency was
examined. Findings show that gender, age, sexual orientation, ethnicity, and disability status did
not predict social justice advocacy competency for this sample. Findings may suggest that
demographic variables such as gender, age, sexual orientation, and disability status are not
relevant to the development of social justice advocacy competency. This finding is consistent
with Jeon’s (2014) research that did not find a significant relationship between demographic
variables and social justice advocacy among rehabilitation counselor trainees enrolled in an
internship course. Other research has reported similar findings (Beer, et al., 2012; Luu, 2016).
In contrast, Wendler and Nilsson (2009) found that participants who identified as lesbian, gay or
bisexual had higher social justice advocacy competencies. Also, implications from the findings
of current study should be done with caution since some of the variable groups were not
balanced; the majority of the participants identified as female (77%), heterosexual (85%),
Hispanic/Latino (58%), and no disability (76%). Although this demographic sample is typical in

88
social behavioral and counseling research; further research with a more balanced sample is
recommended.
RQ5
The influence of counseling training with variables such as classification, completed
internship, completed social justice advocacy course, and counselor program on social justice
advocacy competency was examined. Findings for this study indicate that completing a
practicum/internship course and a social justice advocacy course statistically significantly
increased social justice advocacy competency score, but Master level classification had an
inverse effect on the social justice advocacy score. This suggests that practicum and social
justice advocacy course increases scores on social justice advocacy competencies. This result is
consistent with previous research that indicates social justice education improves social justice
advocacy competency (Kilbane et al., 2014; Linnemeyer et al., 2018; Toporek & Worthington,
2014). In contrast, Killian (2017) reported that counseling pedagogy community service
learning, didactically focused, and experientially focused) did not advance social justice
advocacy competency. In regards to classification, findings suggest that social justice advocacy
development may be predicted by the classification of the counselor trainee. For this sample,
participants who identified as Doctoral level had statistically significantly higher scores versus
Master level; this implies experience and training may predict competency. This is an interesting
finding since the majority (n = 102) of participants identified as Master-level and 24 identified as
Doctoral level counselor trainees.
Other important findings from study are reported in the following segment. There was a
significant difference in social justice advocacy competencies scores between those who reported
yes for professional licensure status and those who reported no professional license. This

89
implies continuous educational training to maintain a professional license also increases social
justice advocacy competencies. In addition, there was a significant difference in social justice
advocacy competencies scores between those who reported their advocacy had been evaluated
and those who reported no. The finding implies that those whose advocacy was evaluated may
be enrolled in a comprehensive counseling program that is implementing social justice advocacy
in the curriculum and training, thus, is more likely to demonstrate higher social justice advocacy
competencies. Another observation, more than half (52%) of participants reported that their
counseling program was CACREP accredited, (55%) reported they have not completed a stand-
alone Ethics course, (80%) have not completed a stand-alone advocacy course, and (77%) have
not evaluated their advocacy competency. It appears this sample has limited social justice
advocacy training even though they are enrolled in a counseling program that is expected to
integrate social justice advocacy. This finding is consistent with a study by Ramirez Stege et al.
(2017) that found there is a lack of advocacy training and assessment of advocacy competencies
in counselor education. However, another explanation for the limited training reported may be
that the majority of the sample are new graduate students and have only started their degree plan.
Mix results have been reported and more research in this area is warranted to determine what
factors improve social justice advocacy. For instance, one study found that the majority of
counselor trainees (71.3%) reported satisfaction and comprehensive social justice training from
counseling education (Decker, 2013).
Limitations
Limitations must be evaluated when drawing conclusions from this study. One limitation
of this study is that it used self-reported measures to collect data. It is possible that participants
might have over or underestimated their abilities in social justice advocacy; therefore; they may

90
have reported their perceptions and not actual ability. Other limitations of the study are related
to the participants. In particular, the participants included 132 counselor trainees who identified
their counselor program as rehabilitation counseling (n = 77), social work (n = 26), counseling
(education) (n = 14), counseling (psychology) (n = 3), human services (n = 1), other (n = 6) from
three different states. Counselor trainees from other disciplines were not represented and other
states were not reflected in the sample studied. Consequently, generalizability is limited and the
results should be viewed with caution when considering application. Also, the majority (80.3%)
of participants reported they were enrolled in a counseling program that is accredited, thus, the
results of this study may only be generalized to counselor trainees enrolled in an accredited
counseling program. Implications from the findings of current study should be done with
caution since some of the variable groups were not balanced; the majority of the participants
identified as female (77%), heterosexual (85%), Hispanic/Latino (58%), and no disability (76%).
Additionally, the study did not reward or offer incentives to participants, and the students who
participated were likely more interested in the topic of advocacy.
Implications and Recommendations
Given the prevalence of disability in the United States, competent rehabilitation
counseling services are critical. The results of the study contribute valuable and practical
information for counseling education, preparation, research and counselor trainees. This study
explored the demographic variables, counselor training, and advocacy training of counselor
trainees and the relationship between these variables and social justice advocacy competency.
Self-perception and reporting of competency is an important element of actual competency. To
facilitate social justice agents in counseling, it is important to investigate the strengths and needs
of counselor trainees. Implications and recommendations for counselor training are discussed.

91
Furthermore, it is noted this was an exploratory study and more research is needed to provide a
comprehensive list of implications and recommendations.
Implications for Counselor Training
This study found that there is a relationship between counseling training and social
justice advocacy competency, while, variables such as gender, sexual orientation, age, ethnicity,
and disability status did not have a relationship with competencies. More specifically, variables
such as classification, licensure status, internship status, whether competencies have been
evaluated, and advocacy course status promote proficiency in social justice advocacy
competency. This finding suggest counselor and advocacy training facilitates competencies in
social justice advocacy. This study also found a significant positive association between the
ELQ and ACSA. The ELQ was used to measure ethical awareness and the ACSA was used to
measure social justice advocacy. Findings of study imply that comprehensive counseling
preparation supports competencies of social justice advocacy; however, it also implies there are
limitations to as counselor trainees have not achieved competency is all social justice advocacy
domains. Therefore, it is recommended that counseling training emphasize professional
development such as licensure/certification, comprehensive internships, and the assessment of
social justice advocacy. Toporek and Worthington (2014) found that service learning with social
justice opportunities build advocacy skills and facilitate a social justice orientation. Another
study also found that integrating a social justice advocacy supervision approach during
supervision was a successful way to prepare social justice advocates (Glosoff & Durham, 2010).
Counselor trainees demonstrated the need for more preparation in particular levels and domains
of social justice advocacy, for example, systems advocacy, public information and
social/political advocacy. Thus, it is critical that counseling training integrate social justice

92
advocacy both in theory and practice. Ratts and Greenleaf (2018) report there is a lack of
emphasizes on social justice and social political advocacy presented in counseling training and
propose that social theories, models and interventions be integrated in counselor preparation to
support the development of comprehensive social justice advocacy.
Program recommendations
It is recommended that counseling programs promote a social justice climate. Hudson,
Shapiro, Ebiner, Berenberg, and Bacher (2017) reported programs that engage in social justice
practices within classrooms and program’s policy facilitate a social justice professional
orientation among students. Another suggestion for educators and programs is to highlight social
justice advocacy as a core value of professional counseling. For example, a program can include
competencies in social justice advocacy as a component in the admission to counselor program
process and in the counselor comprehensive examination. Ramirez Stege, Brockberg, and Hoyt
(2017) examined the advocacy skills of counselors and reported that assessing advocacy
competence during counselor education improves confidence and competency.
Curriculum recommendations
It is recommended that counselor curricula integrate a stand-alone social justice
advocacy course and implement the ACA advocacy competencies as a model to enhance
counselor trainees’ confidence and skills. Harris, Owen, and De Ruiter (2012) found that
classroom activities such as meetings with legislators, writing letters to law makers, and leading
community presentations increased confidence and competencies in systems advocacy. Other
research echo similar findings about counselor curricula, for example, Bemak and Chung (2011)
found that courses which incorporate service learning along with supervision, and mentoring
increase motivation and confidence to engage in social justice advocacy. This also includes

93
course discussions and projects that explore topics of privilege, oppression, and advocacy (Hays,
Dean, & Chang, 2007). Thus, social justice advocacy is a learned skill and counselor curricula
that integrates social justice advocacy can facilitate social justice agents.
Future Research
An exploratory study was conducted to address the lack of empirical research that
explored the competencies of rehabilitation counselor trainees in social justice advocacy.
Implications and recommendation were identified and discussed based on the study’s findings.
However, in order to provide comprehensive implications, future research may want to explore
the variables attitude toward and knowledge about disabilities as a predictor in competency to
engage in social justice advocacy. Stuntzner and Harley (2014) stress the importance of
counselors that work with individuals with disabilities to be well informed and trained on the
experience and process of disability in order to be effective counselors. Another suggestion is
for future research to examine the relationship between social justice advocacy and the
counseling programs’ curricula and counselor program accreditation status. Hudson, Shapiro,
Ebiner, Berenberg, and Bacher (2017) recommend research to expand on their study and
examine the curricula of other counseling disciplines and their approach to social justice
advocacy training.

