


Introduction dissertation as well as the main focal
This chapter introduces the scope of the dissertation as well as the main focal
points of the research. The rationale for this research will be discussed, as will the
research questions, their significance to the health and well-being of the research
population, and the implication of the study in terms of health care services and practices
among adivasi groups in India.
Statement of the Problem
Belief systems and practices related to concepts of sickness, health, and healing
are found in all cultures worldwide. How people within a specific cultural group define
health and sickness, wellness, and disease is influenced by a variety of factors. This
dissertation examines the health care and healing belief system and practices of the
Rathwa adivasi (original inhabitants, tribal group) of Kadipani village in Gujarat State,
India. The study includes an examination of Rathwa concepts and beliefs about sickness
and health, as well as a discussion of the pluralistic health care system available to them.
I include an explication of the various ethnomedical (indigenous/folk medicine,
Ayurveda, homeopathy) and biomedical (science-based medicine) health care systems
Rathwa have access to, both in Kadipani village where they live, and in Kawant, a
neighboring village where numerous private and public health care providers are located.
My primary purpose was to determine the degree to which ethnomedical and biomedical
health care systems accessed by the Rathwa intersect, and what factors encourage or
discourage this intersection.

In addition to studying Rathwa health care and healing practices, this research
also investigates household health care decision making processes, including an
examination of those variables specifically related to health care seeking behavior. For
the Rathwa, this involves issues based in religion, economics, and tradition. I examine
how the Rathwa deal with illness, including determining which provider(s) to use for
health care, either singly or in tandem, who within the household receives what type of
treatment, and what type of home remedies to use from locally grown medicinal plants.
I specifically considered Rathwa health care and healing practices specific to malaria and
sickle cell disease.
My research provides information on the processes that the Rathwa go through
when dealing with health-related issues; how and why they value certain health care
providers over others; when they may seek the services of a specific type of
practitioner; where they go for health care services (e.g., Kadipani village ethnomedical
practitioner, Kawant government or private clinic, etc.); and why they make specific
health care choices. This study reveals information not just about what the Rathwa do
when they or a family member is sick, but how their history, culture, and beliefs
systems may be impacted by changes related to modernity.
Rationale
This research is an ethnographic study of the health care and healing practices
utilized by the Rathwa, with a specific focus on how they prevent and treat malaria and
treat sickle cell disease, especially when someone is in sickle cell crisis. The Rathwa
were selected for inclusion in my research for three reasons: (1) they are the largest

adivasi group in the area; (2) a large percentage are estimated to have sickle cell disease
(S. Basu 1992; Dr. Vijay Shah, personal conversation June 2007), a critical factor in the
study of health care practices of people living in a malaria-endemic region; and (3) the
pluralistic system of health care in Kadipani and Kawant villages provide an ideal
environment for investigating how people navigate and negotiate such a system within
the boundaries of their cultural belief systems about sickness and health.
Of special interest to this research is the fact that the Rathwa have historically
used indigenous faith healers called bhouas for dealing with health-related concerns. With
the availability of biomedical health care services, and the Indian government’s
promotion of programs designed to encourage Rathwa utilization of biomedical health
care services (e.g., institutional deliveries, inoculations for children), I hypothesized that
there would be a trend away from using indigenous/folk medicine practitioners such as
bhouas or traditional birth attendants, and an increase in Rathwa accessing biomedical
health care services available at the public sector clinics and hospital.
My research considers not only the pluralistic health care system, or “health
cultures,” within Kadipani village and neighboring Kawant village, but also situates the
problem of meeting one’s health care needs (the micro perspective), within the larger,
macro perspective of a changing economic context. This context is being influenced by
increasing uncertainty related to natural resources, specifically access to water from the
Narmada River, the mining of fluorspar and other minerals by GMDC, a large operation
in Kadipani. These two factors potentially could have an impact on Rathwa health status
and quality of life in ways such as differential access to health care.

Terminology—Adivasi, Tribe, Tribal
The terms tribe and tribal are contested terms in anthropology. I will use the term
adivasi instead of tribe or tribal when referring to the Rathwa as that is how they refer to
themselves. Tribe and/or tribal will be used only when referencing another author’s
work. The term adivasi is derived from two Sanskrit words: adi (original) and vasi
(inhabitant). Adivasi are variously defined as original people, original inhabitants, or
indigenous peoples (Bailey 1960; Baviskar 2005, 2006; Bayly 2001; Karlsson and Subba
2006), or as aborigines (Baviskar 2006), or as old settlers (K. S. Singh 1995:31). Adi
may also mean beginning, or of earliest times, and vasi, meaning resident of.
The Rathwa Adivasi of Kadipani Village
The Rathwa adivasi of Kadipani village reside in a rural, hilly, forested region of
Gujarat State, which is in the northwest region of India. This area is populated by other
adivasis (Bhils, Nayaka) as well as non-adivasi people, who live in villages of varying
sizes, where they practice an agrarian life-style that includes crops such as corn and the
tending of various livestock. Being patrilineal and patrilocal, the Rathwa live in joint
families in small houses made of wood, cow dung, and occasionally bricks on plots of
land that they own rather than lease or rent. Households have few amenities. There is no
indoor plumbing or sewer system in Kadipani. Most homes were clustered around water
sources.
The Rathwa practice Hinduism, with many homes having altars in a special corner
to honor different gods and goddesses. There is also a large temple to the god Shiva, and
a smaller temple to the god Ganesh and local deities in the center of the village, both of

which conduct early morning services. The Narmada River, which is not far from
Kadipani, is considered a goddess in Hinduism, and figures prominently in various
religious ritual practices, which I will discuss in detail in a later chapter. Rathwa women
tend to be more spiritual than Rathwa men. They maintain altars in the home, conduct
spiritual rituals, and frequently report visiting the temple for healing when faced with
health and other personal and family problems.
The Kadipani economic base is primarily agrarian with most families practicing
some type of farming as well as raising livestock such as bullocks, cows, goats, water
buffalo, and chickens. A few households supplement their farming income by operating
small shops where they sell household staples, fruits and vegetables, tobacco products,
and personal care items (e.g., soap, combs, toothbrushes). Others seek outside work such
as labor at the Gujarat Mineral Development Corporation (GMDC), a mining operation
located in Kadipani, where they hold labor, security, driving, or welding positions. Some
men have migrated to other areas in search of construction work—an option that is
becoming more prevalent. GMDC, whose operations were off line during my
preliminary visit to the field site in June 2007, began operations again in the fall of 2007
and remained in operation during the duration of my field research.
Recognizing the impact of GMDC operations on the local economy (employment
for Rathwa men, migration of people from other communities to Kadipani to work for the
mine), and the prospect of damming projects along the Narmada River, this study of
Rathwa health care and healing practices is primarily a medical anthropology study, but
considered within the context of development anthropology.

Introduction to the Research Site and Methods
My research began with a preliminary visit to the field site in June of 2007,
followed by intensive fieldwork and data collection from November 2007 through
February 2008. Field research was conducted in Kadipani village, where the Rathwa
reside, and Kawant village, which is approximately 13 kilometers from Kadipani, the
main place where the Rathwa go for public as well as private sector health care services.
My research was sponsored by Dr. Vijay Shah of the Indu Blood Bank in Baroda, a city
about two hours drive from Kadipani. I lived in Kadipani at the GMDC guesthouse
during my data collection.
Translators were used to facilitate the data collection process. I spent a
considerable amount of time prior to entering the field searching for a translator(s). I
needed someone who was fluent in both English and Gujarati, who could understand my
American English accent, and with whom I could clearly communicate. I also needed
someone with a flexible schedule, who was willing to live with me in the field, and was
comfortable speaking with adivasi and asking health-related questions. I interviewed a
number of perspective candidates, most of whom were ruled out because their English
skills were inadequate, they were unwilling to live with me in the village, or they wanted
to be paid a considerable sum of money for their work.
I selected two young women to be my translators. Ankita Patel and Hatel Patel
were classmates at Dr. Vijay Shah’s college. Ankita and Hatel were on a break from
school during the time I needed translators, so the arrangement worked well for all of us.
I interviewed both Ankita and Hatel at their college. We spent time talking, and I

explained my research project. Since they were both microbiology students, the
opportunity to conduct health-related research interested them. I also spoke with their
parents and obtained permission to take their daughters with me to the field. I met
Ankita’s father in person the morning we were to leave for Kadipani, and spoke with
Hatel’s father again once we were in the field. This is significant to mention as Indian
families are very protective of their daughters, and I had to assure these parents that I
would properly supervise and care for them.
I had been informed by my mentor, Dr. Vijay Shah, that the local dialect of
Gujarati changes every 12 villages. I was concerned about this because my translators
were not adivasi, nor were they locals—they were from the city of Baroda, which is about
2–2.5 hours drive from Kadipani and Kawant villages. I did not know if they would be
able to communicate with the Rathwa in Gujarati and be fully understood. I was also
curious if there would be issues related to differences in status. My translators were part
of the Hindu caste system and the Rathwa were not. I had been told by one individual
prior to leaving for the field that I “would not find anyone willing to live with me in the
field” because that is not something that non-adivasi people do. Fortunately, I was able
to find two translators willing to live and work with me during my time in Kadipani and
Kawant.
Prior to beginning any formal interviewing or surveying, I trained my translators
on how we would conduct our research. We practiced asking the questions on both the
interview schedule and villager survey form using different Gujarati speaking volunteers
until I was satisfied that the information was being conveyed accurately in both directions

—my English to their Gujarati and back again. There is the possibility that some
meaning may have been lost in translation, but I believe that the information and data I
obtained is accurate. I had three different English and Gujarati speakers review both the
completed interview schedules and survey forms for accuracy, as well as problems with
meaning or translation.
Since ethnographers typically have access to what people say, do, and leave
behind (Schensul et al. 1999:1), I selected data collection methods that would give me an
in-depth look at what the Rathwa do when someone is sick, why they do it, and what it
all means within the framework of their belief system and cultural practices. I was
concerned about respondents understanding what I was asking—would certain concepts
translate linguistically as well as culturally? I also was concerned about whether they
would tell me the truth, or tell me what they thought I wanted to hear, especially when
discussing their use of traditional/folk medicine.
My methods included: surveying Rathwa households in Kadipani (n = 121);
formal interviews with both ethnomedical and biomedical health care practitioners
(HCPs) in Kadipani and Kawant (n = 19); formal interviews with a sample of Kadipani
villagers (n = 30); informal interviews with Rathwa, HCPs, local government officials,
GMDC administrators and workers, and participant observation in a wide variety of
settings in both Kadipani and Kawant (e.g., public clinic and hospital, private clinics,
villagers’ homes, markets, temples, village center, local shops, primary school).
Since the Rathwa receive health care from a variety of ethnomedical and
biomedical service providers in the private or public sectors, local providers of all types

were included in the research (e.g., Bhouas, Ayurvedic, homeopathic, and allopathic
doctors.) There were no Unani tibb practitioners in either Kadipani or Kawant. Unani
tibb is an ethnomedical health care practice found among Muslim populations. Public
sector services are provided free of charge, while health care services at private clinics
are provided on a fee for service basis. I spent extensive time observing in private clinics
and the public clinic and hospital, which allowed me to see a wide range of illnesses
being treated.
Research Questions
1. What prompts Rathwa to seek a certain type of health care, be it
ethnomedical, biomedical, or a combination of both?
2. Do Rathwa forgo ethnomedical practitioners and instead visit a biomedical
practitioner when faced with disease or illness? If so, what factors influence
this decision?
3. If there has been an increase in Rathwa accessing biomedical services, which
diseases most frequently result in visits to biomedical practitioners (e.g.,
malaria, sickle cell disease, fevers, childbirth, broken bones, etc.)?
4. What impact do traditional gender practices have on health care decision
making?
5. What is the impact of economic development projects in the region where the
Rathwa live on health care decision-making, especially as it relates to
household income and socioeconomic status?

Structure of the Dissertation
Chapter Two begins the dissertation with an introduction to the research setting,
Gujarat state, geography, demography, health care practices within the country, a
discussion of malaria and sickle cell disease, and prior research. Chapter Three is a
discussion of theory including social constructivism, political economy, feminist, and
modernization. I focus on how the local political economy impacts health and health care
seeking behavior; the influence of Rathwa socially-constructed beliefs about sickness and
health; gender-based differences health care and healing; and the role of modernity in
choice of health care provider. Chapter Four provides a lengthy explication of
ethnomedical and biomedical health care practices among the Rathwa, as well as a
discussion of the spiritual or religious aspects of health care and healing. Chapter Five
covers the methodology I used for data collection, including the sampling procedures, key
informants, and reflections on my fieldwork experience.
Chapter Six includes my data analysis and a discussion of findings, including an
examination of the barriers to health care, socially constructed beliefs about sickness and
health, and the changing perceptions and roles of health care providers. Chapter Seven
discusses my major conclusions, addressing the five research questions and offering
recommendations to address specific Rathwa health concerns (with a specific focus on
prevention, treatment, and education programs for both malaria and sickle cell disease.
Chapter Eight completes my dissertation by examining the contributions of my research
to applied anthropology and to health care in India. Three separate sections specifically
address health care and healing; the local political economy; and Rathwa identity, both as

Rathwa and as adivasi.

CHAPTER TWO
THE RESEARCH SETTING: GUJARAT STATE, INDIA;
HEALTH CARE PRACTICES; MALARIA, SICKLE
CELL DISEASE AND PRIOR RESEARCH
Introduction
This chapter discusses Kadipani and Kawant villages, situating these communities
within the larger context of Gujarat State, and the country of India. Since India is a
developing nation, I examine how development in the region may be impacting life for
the Rathwa in Kadipani village, as well as how health care in India has evolved over
time, and current health care and healing practices.
Research Setting
Kadipani and Kawant villages are in a rural part of Gujarat State, and are ideal
locations for conducting this research on ethnomedical and biomedical health care
practices among an adivasi group. India has the largest tribal population in the world,
consisting of approximately 67.7 million (Tewari 2004:161), with adivasi groups
comprising about 8.08 percent of the total population (Kshatriva 2004:17). In addition,
people in the area have a long history of practicing ethnomedicine, though they are
increasingly exposed to biomedical health care services through health-related programs
such as institutional births, inoculations for children, and government-sponsored health
education projects, such as family planning.
While Gujarat State is very modern and urbanized in many areas, Kadipani and
Kawant are rural, with most people living in small villages with governance and health

care system provision being provided at the local village, taluka, and district levels, as
well as the overarching national level. India, a former British colony that achieved
independence in 1947, is a rapidly developing nation, undergoing changes in many arenas
(e.g., political, economic, education, health), especially in the realm of the provision of
health care services to its diverse population groups.
Geography
Gujarat State is located in the north-west portion of India, and has a border with
Pakistan. Gujarat is a particularly significant location for this dissertation research
because even as it ranks as one of the most developed states in India, in terms of both
agricultural and industrial growth, this growth has largely been concentrated in central
Gujarat. The extent to which this growth will impact the southern part, which is home
to a variety of adivasi groups, and forms part of a larger adivasi population stretching
through central India, is a process that remains to be documented.
Demography
Gujarat has a population of approximately 50.5 million (Census of India 2007),
of which about 15 percent are classified as members of “Scheduled Tribes” (ST). The
Rathwa are classified as ST (N. P. Das 2000) and are afforded certain social, economic,
and educational rights due to this status. This research was conducted in Kadipani and
Kawant, neighboring villages located in a rural part of Gujarat State (Figure 1—Map of
Gujarat State).
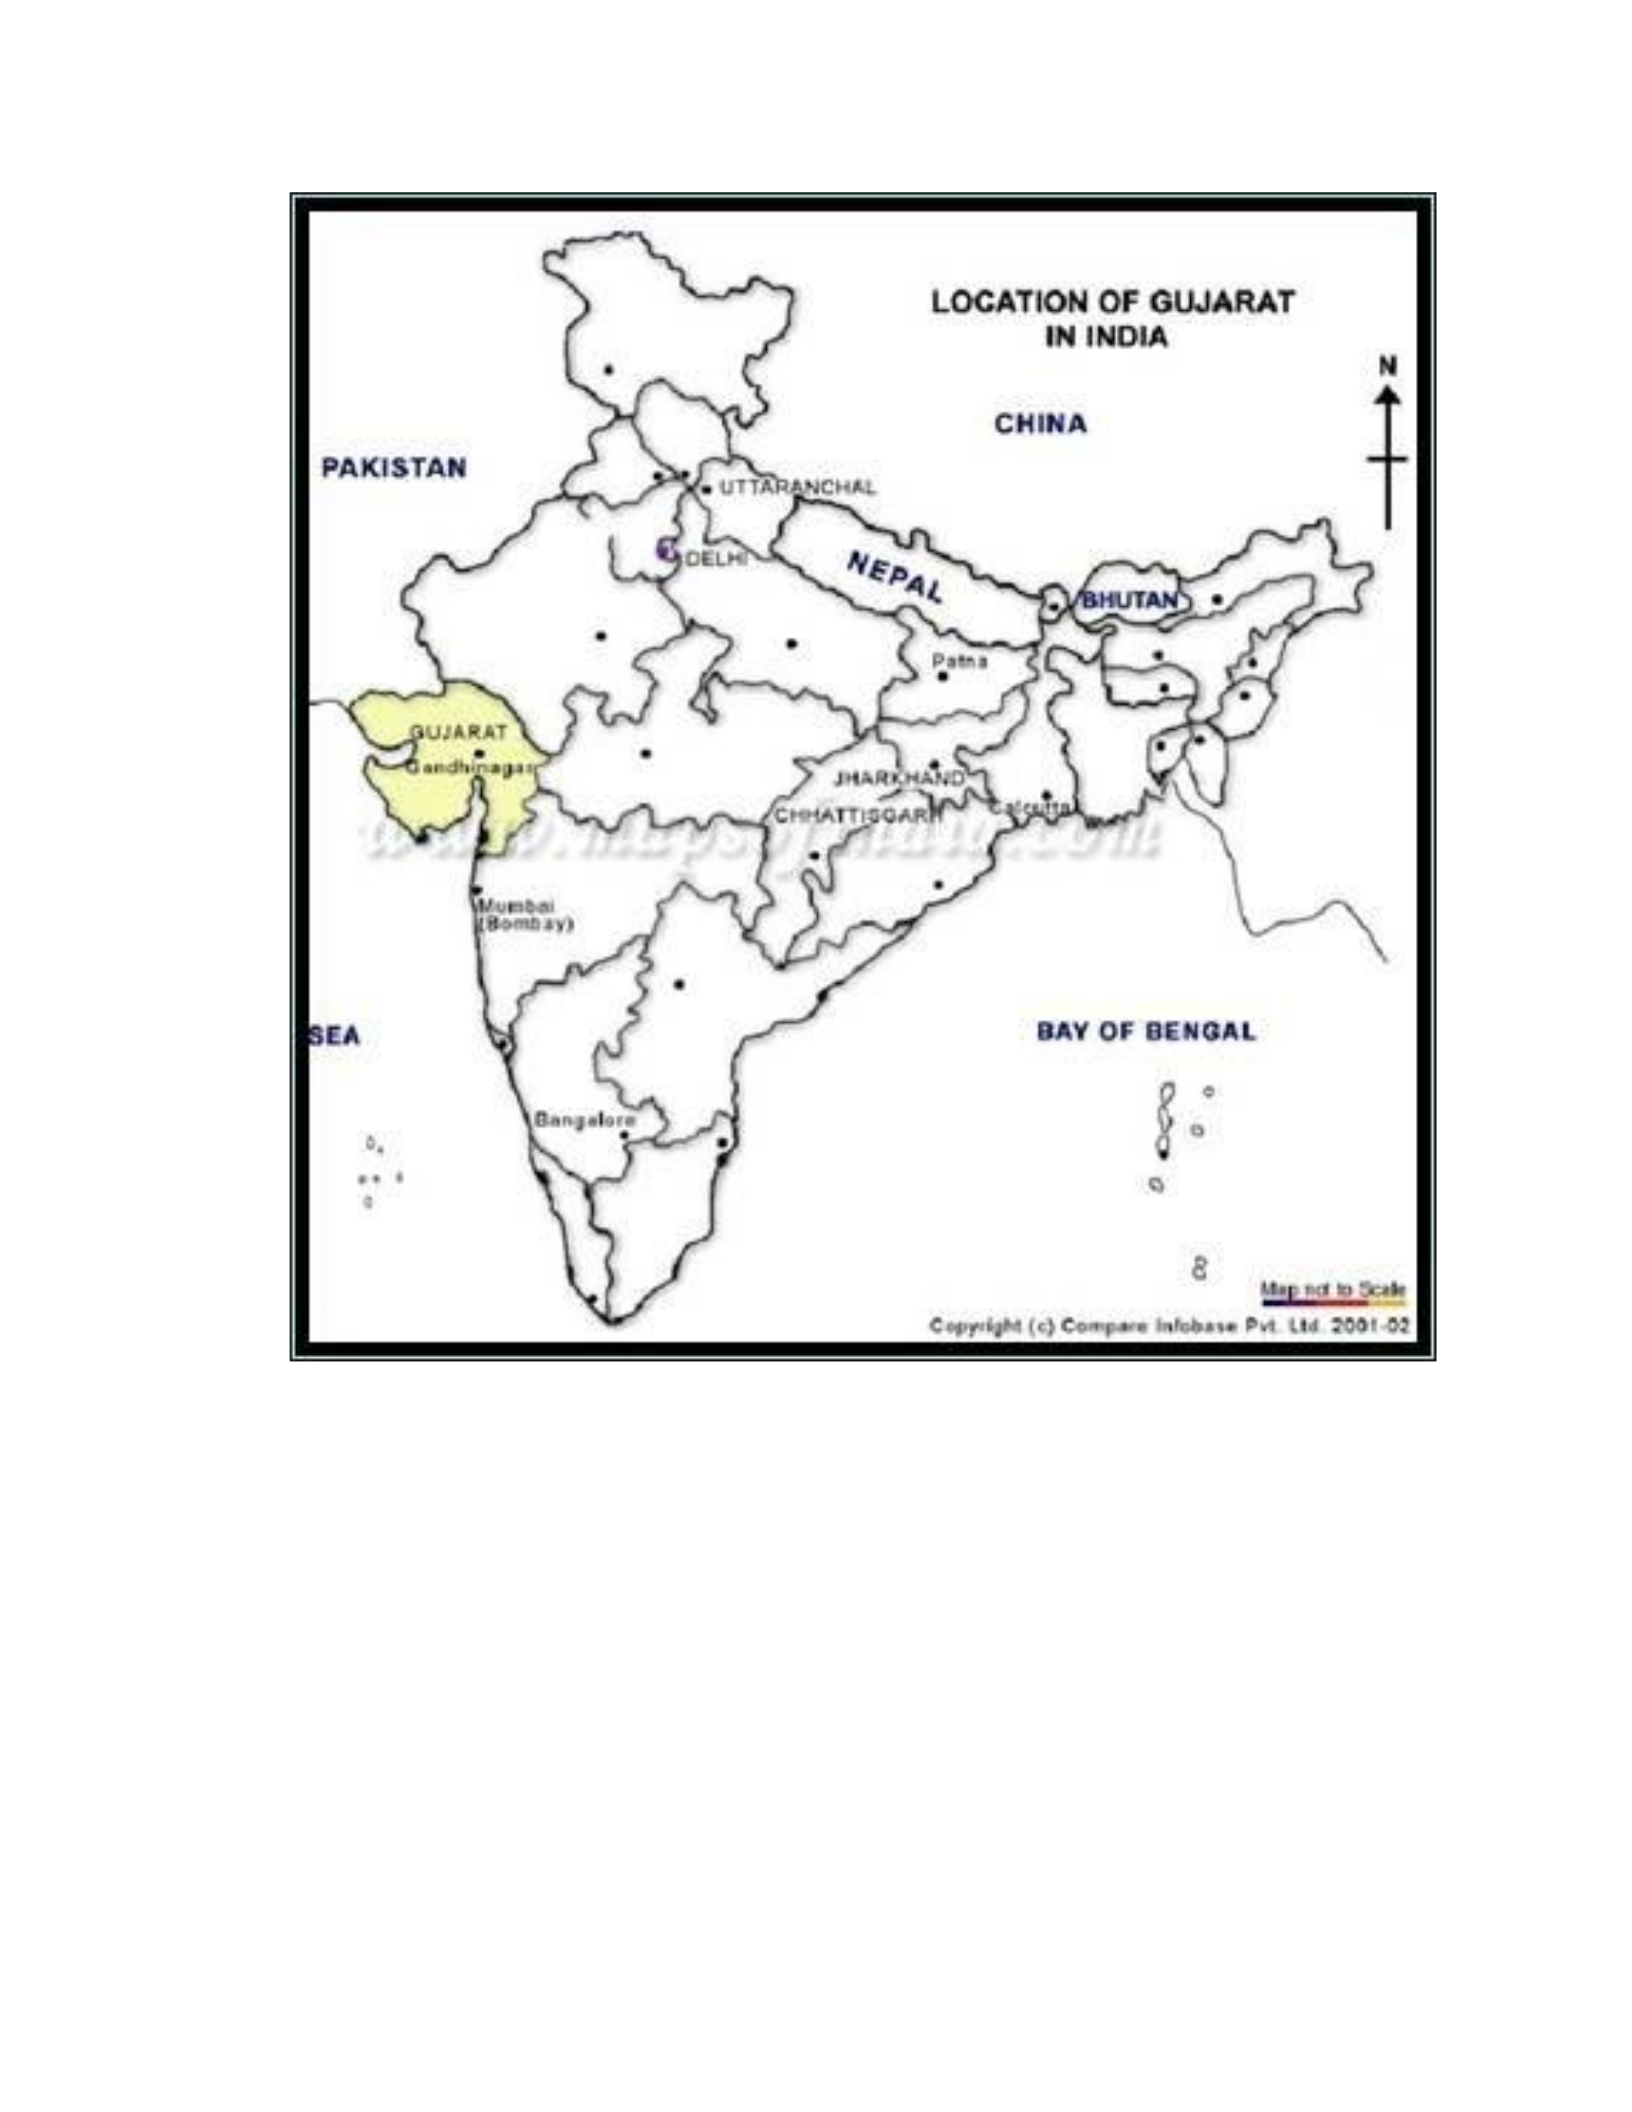
Figure 1. Map of India. Gujarat State is in yellow (Grouptrust.org 2009).
Kadipani and Kawant are situated in a hilly forest area where there has been
an increase in industrialization, including fluorite mining by the Gujarat Mineral
Development Corporation (GMDC), as well as damming projects along the Narmada
River (Figure 2), which has resulted in numerous changes to established adivasi
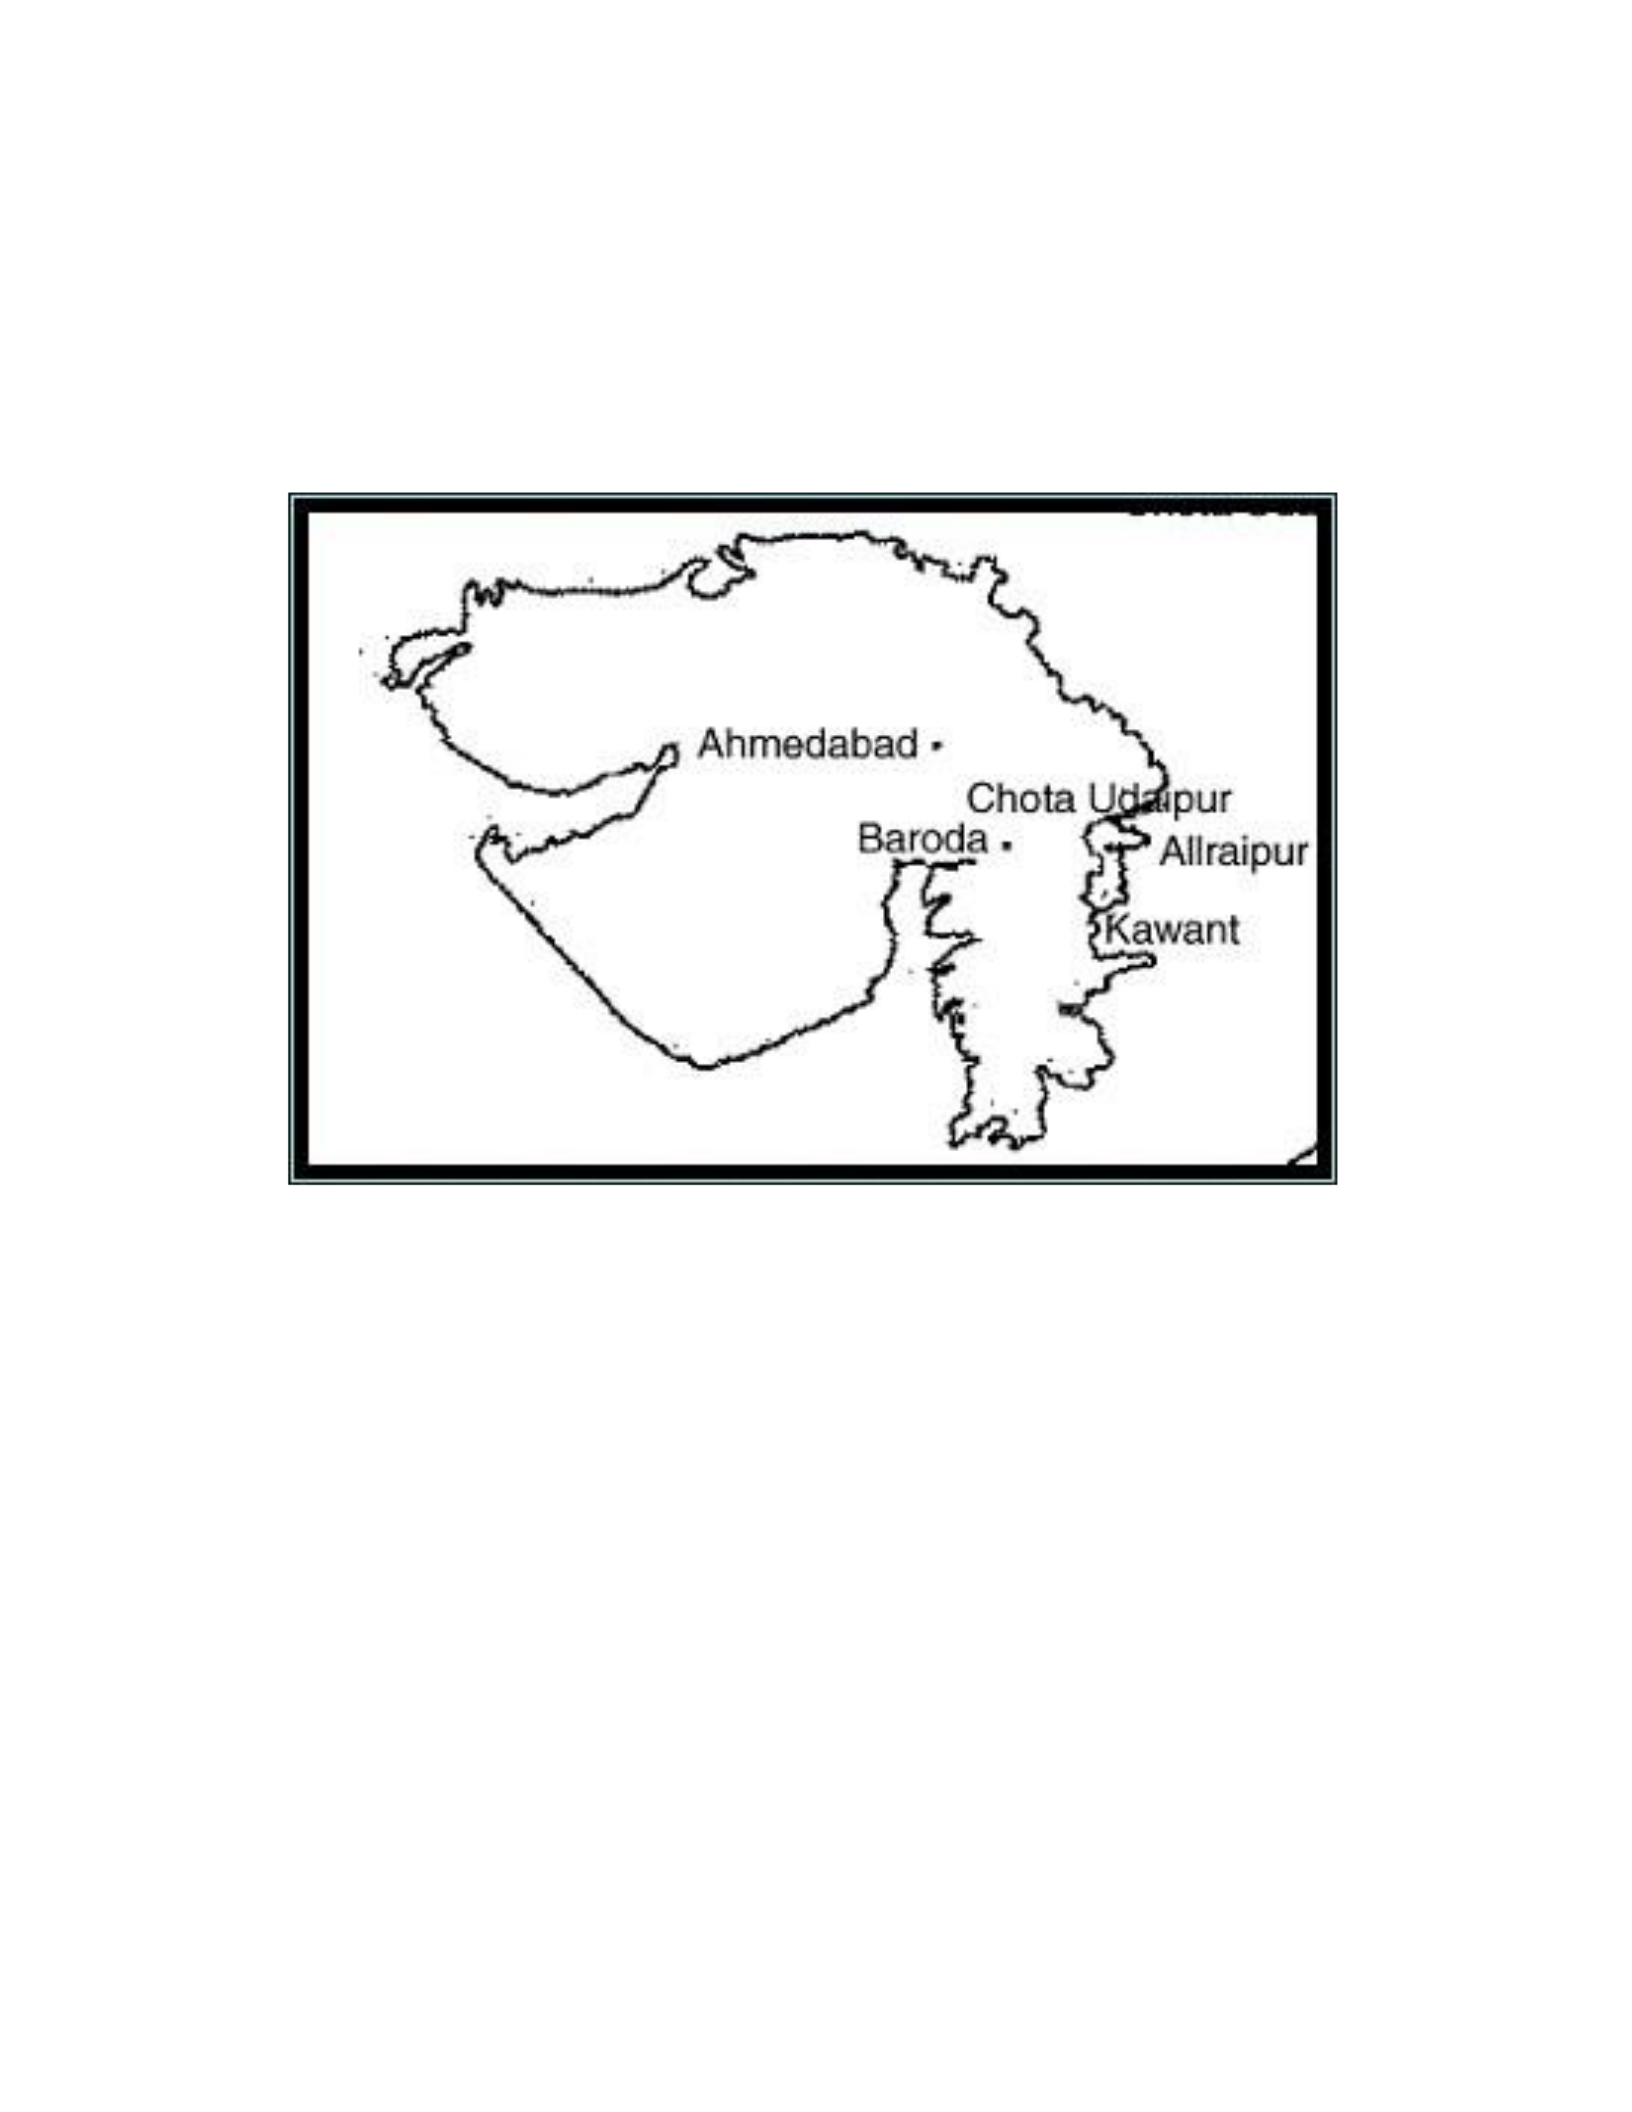
lifeways, including the flooding of entire villages, the dislocation of homes, loss of
farm land, an increase in outward migration for employment, and an increase in the
prevalence of certain diseases (Blinkhorn and Smith 1995; Deegan 1995; Fisher
1995a, 1995b; Khagram 2004; Kothari 1995; Patel 1995).
Figure 2. Map of Gujarat State showing Kawant village (Pandya 2004:118).
The Narmada River
The Narmada River has an interesting history and mythology. Described as “swift
and meandering,” the Narmada flows east to west, covers approximately 800 miles, and
passes through three states (Maharashtra, Madhya Pradesh, and Gujarat) before emptying
into the Gulf of Khambhat which flows into the Arabian Sea (Deegan, 1995; Fisher
1995a). As a naturally occurring “geographic and cultural boundary from both northern
and southern perspectives” (Fisher 1995a:31), the Narmada may be seen as a dividing

line both culturally and historically. Interestingly, “coordinated development through big
dam building on many of India’s waterways was originally investigated and planned by
British authorities during the colonial period” (Khagram 2004:34). After independence
from British rule, when faced with severe drought in the 1960s, the Indian government
sought ways to ameliorate this situation, with the primary solution being the construction
of dams along the Narmada. The problems that ensued are widely chronicled; many
remain today (Blinkhorn and Smith 1995; Khagram 2004), and will continue as long as
damming projects remain an option for national development.
The Narmada River, which has been “targeted for ‘water resource development’
for more than fifty years now . . . has, until recently, evaded being captured and
dismembered” because it courses “through three states—Madhya Pradesh, Maharashtra
and Gujarat” (Fisher 1995a:31). Conflict among the three states over water sharing
programs has resulted in a slowdown in the implementation of a number of damming
projects (Figure 3). Fisher (1995a) writes on development projects along the Narmada
River and subsequent resistance to these projects by adivasi groups. He notes that the
Narmada conflict has been “frequently portrayed in the press as a struggle between a
powerful multinational development apparatus, on the one side, and relatively weak and
defenseless local nongovernmental organizations, on the other” (Fisher 1995a:15).
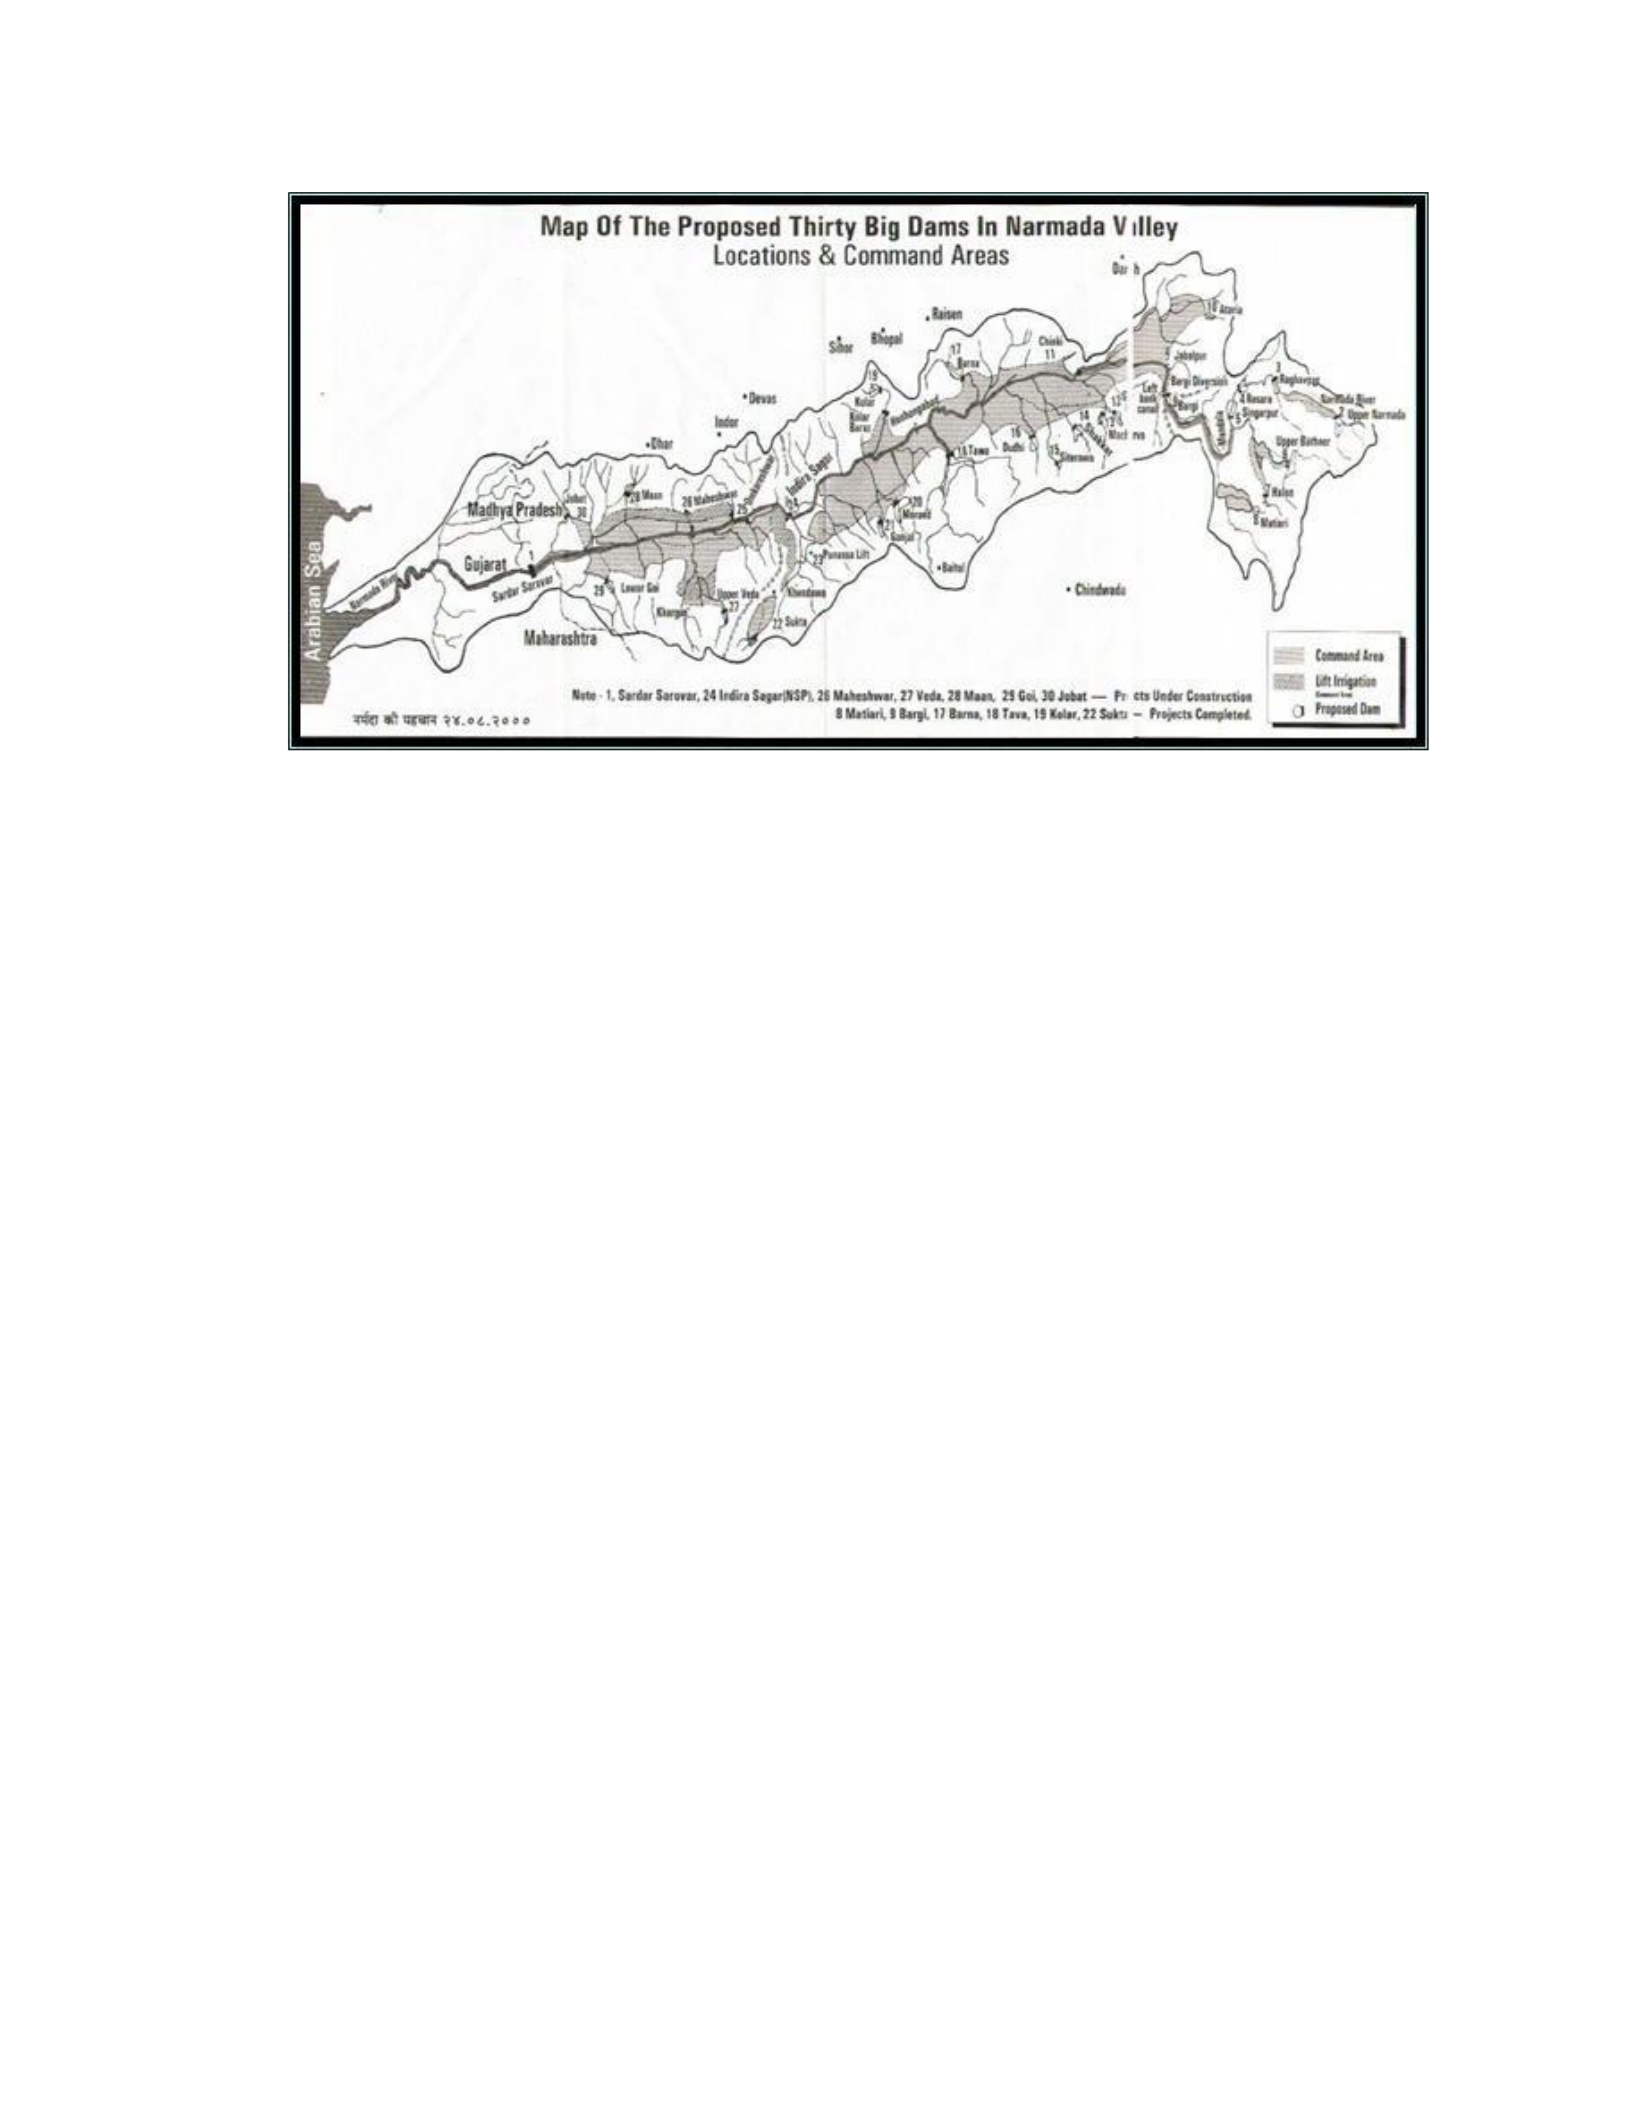
Figure 3. Map of the proposed thirty big dams in Narmada Valley (Friends of River
Narmada 2007:n.p.).
What is absent is the voice of the adivasi groups who live along the Narmada and
who have been displaced by the damming projects. The stress of dealing with such an
issue could potentially affect peoples’ health. Patel asks a critical and difficult-to-answer
question: “What do the Narmada Valley tribals want,” when it comes to economic
development, land rights, access to water, and recompense for lost livelihoods resulting
from damming projects (Patel 1995:179). Various plans for remunerating people for lost
land, livestock, and household goods have been proposed but not always implemented.
What results is a growing group of displaced people who have no land, with women
being especially impacted due to “a patriarchal notion of landownership being imposed
by the state on tribal societies” (Basu and Silliman 2000:431).
Baviskar (2005) writes on adivasi conflict over damming projects along the

Narmada River, noting that longstanding issues pertaining to power differentials, access
to water, and loss of land and livelihood continue today. Arundhati Roy, an Indian writer
and activist who has chronicled the progress of Narmada River damming projects during
the 1990s observes that “India is the third largest dam builder in the world” and that
“their reservoirs have uprooted millions of people” (Roy 1999:ix), including the Rathwa
(personal communication with displaced villagers, June 2007). While dams have “been
built in the name of National Development” (Roy 1995:ix), the impact of these damming
projects on adivasi groups is extensive and far reaching, including flooding of villages
and the resultant displacement of people, as well as the loss of livelihood from the
subsequent loss of farmland, homes, livestock, and material possessions critical to
carrying out one’s profession. The Narmada River, which courses through Gujarat state,
is in close proximity to where the Rathwa live, being a source of water for cooking and
drinking for some villagers. I discuss the significance of this in detail later in the
dissertation.
The Local Economy
Development initiatives in Gujarat are varied, but the largest and most
controversial include the damming projects along the Narmada River (Basu and Silliman
2000). Khagram notes that “great numbers of big dams were initiated right at the very
start of the post-Independence era” (Khagram 2004:35), and have been ongoing and
controversial. Damming projects along the Narmada River continue today with the

Sardar Sarovar project perhaps being the most controversial, with groups of all types,
(governmental, NGO, special interest, etc.) entering the fray. Resettlement programs for
those displaced by newly constructed dams and the subsequent flooding have resulted
in massive loss of land and livelihood, and have not always been successful, doing little
to ameliorate problems faced by powerless, displaced villagers. For the Rathwa,
development of the local economy is impacted by uncertainty regarding access to water
from the Narmada River and GMDC mining operations.
Nagla notes that in pre-Independent India “the dominant system of medicine was
the traditional system which had no preventative characteristics and its effectiveness for
controlling diseases was very slow and inadequate” (Nagla 1997:60). Unfortunately,
such long-standing practices which persist to this day do not always adequately meet the
health care needs of the adivasi populations who live in rural regions, and who might not
be fully receptive to what some refer to as angreji, or English medicine (Hardiman and
Raje
2008:44). S. K. Basu, who writes extensively on adivasi health in India, observes that,
There are more than 400 tribal groups in India who are exposed differently to the
various climatic and environmental stresses/strains and are characterized by their
individual socio-economic, socio-cultural and socio-biological set up. The health
of these adivasi groups is as such a function of the interaction between
sociocultural practices, genetic characteristics and the environment conditions.
The widely varying prevalent health practices, use of indigenous herbal drugs,
taboos and superstitions are also responsible for determining the health behaviour
and health status of the tribal groups. (S. K. Basu 1994a:v)
The World Health Organization set the goal of “Health for All by the year 2000 AD,” the
intent of which was to make strides toward a more equitable delivery of health care

services worldwide (Nagla 1997:7). The Indian government, as one of the signatories to
this declaration, has made an effort to increase the availability of biomedical health care
services to adivasi populations throughout the country (Paul 2005; Tyagi 2002:35). This
is a monumental task, one that entails significant changes to healthcare, what Tyagi refers
to as “nothing short of extraordinary” (Tyagi 2002:35, emphasis added). Unfortunately,
the year 2000 has passed, as has the WHO’s goal for achieving health for all by that date.
Still there are people in numerous countries, including India, and specifically adivasi
groups, who are waiting for some improvement in the health care they receive (S. Basu
1992, 1996; Kalla and Joshi 2004; Lamba and Mehta 1995; Nayak and Babu 2003; Rath,
2004). The “extraordinary” work that is required could well include detailed,
locallyspecific examination and analysis of the relationship between ethnomedical and
biomedical health care systems, as represented in my study.
Mineral Mining in Kadipani Village
During my preliminary visit in June 2007, and again during my fieldwork in
2007–2008, the topic of health repercussions related to excess fluorite in the local water
as a result of mining operations came up as a suggested topic for investigation and
research. Occasionally, an HCP would bring Rathwa children to me and have the child
show me his or her teeth, which were frequently discolored from a medical condition
called fluorosis (Figure 4). It was speculated that children’s teeth and bones, as well as
the teeth and bones of adults in the area of the mine, were being harmed by excess
fluorite in the water that people collect from local wells, hand pumps and taps for
drinking and cooking. During my time in Kadipani, I collected a water sample from a

local hand pump near the center of the village and sent it to a lab for analysis so I could
learn more about how this one environmental factor may be influencing Rathwa overall
health status. I discuss the findings of this water sample analysis later in the dissertation.
Figure 4. Young boy with teeth showing damage from fluorosis.
Colonialism, Development, and Health Care
As a former British colony, “a half century of freedom has tripled India’s
population . . . more than quadrupled its gross domestic product, and lifted its economy
in the last half decade of ‘globalization’ into orbits of cyberspace, armed with nuclear
ballistic missiles and satellite dishes” (Wolpert 1997:vii). With these expansive changes
have also come cultural changes, some beneficial, others not. Burgeoning population
growth has resulted in “estimates of absolute poverty around 34.7 percent . . . absolute

and relative poverty generate extremely unhealthy environmental conditions that are
conducive to disease” (Qadeer and Visvanathan 2004:147).
India has been colonized by Great Britain (“British India,” Princely States),
France (Pondicherry, Chandernagore, Karikal, Yanaon, Mahe), and Portugal (Goa)
(Chamberlain 1998). In 1858, “British India (the presidencies of Bengal, Madras, and
Bombay) passed from the dual government of the East India Company and the British
Crown, wholly to that of the British Crown” (Chamberlain 1998:45). The English East
Indian Company, “opened up India to British trade, governed Bengal for the Mogul
Emperor from 1765, and governed British India in partnership with the British Crown,
1884–58” (Chamberlain 1998:292). In 1876, Queen Victoria of England was
“proclaimed Empress of India” (Walsh 2006:295), with all Indians becoming British
subjects. Those parts of India considered British colonies remained under British rule
until achieving independence on August 15, 1947. In 1961, Goa, which had been a
Portuguese colony, was declared an Indian territory, having been “forcibly taken over”
(Chamberlain 1999:30).
Dirks, who has written extensively on colonialism, states that “colonial conquest
was not just the result of the power of superior arms, military organization, political
power or economic wealth.” Rather, it was “sustained and strengthened, as much by
cultural technologies of rule as it was by the more obvious and brutal modes of conquest”
(Dirks 1996:ix). Colonization “was motivated by the desire for living space or the
extraction of riches” (R. J. C. Young 2001:19), which “depended upon determining,
controlling, and representing the past” (Cohn 1996:3).

Colonialism “has from the very beginning been a contest over the mind and the
intellect. What will count as knowledge? And who will count as expert or as innovator?”
(Shiva 2000:vii). From “the eighteenth century onward, European states increasingly
made their power visible . . . through the gradual extension of ‘officializing’ procedures
that established and extended their capacity in many areas” (Cohn 1996:3) and frequently
resulted in “the transformation of the indigenous economy . . . through the economic and
ideological effects of capitalism into non-capitalist societies” (R. J. C. Young 2001:24).
Colonialism “involved forms of subjugation of one people by another” (R. J. C. Young
2001:15), in a “world . . . full of incentives for accumulation of all kinds, from knowledge
to spices, from narratives to military command posts” (Dirks 1992b:6).
Decolonization is “the surrender of external political sovereignty, largely Western
European, over colonized non-European people” (Springhall 2001:2). Independence
brought about numerous changes in India, not just in governance, but also in all aspects
of Indian life and culture. Colonialism “not only has had cultural effects that have too
often been either ignored or displaced . . . it was itself a cultural project of control (Dirks
1992b:3). Kalla and Joshi observe that,
The independence of India from British dominance however has been a turning
point in India’s destiny and consequently of its tribal inhabitants. The tribal for
the first time became a political entity and were incorporated as sections of
society needing provision in matters concerning education, employment and
political representation. (Kalla and Joshi 2004:xiii)
In the postcolonial moment, much has changed and is changing for India. The
“category or ‘tribe,’ it has been contended, is wholly a colonial construction, as opposed
to that of caste which, apart from its particular construction by the colonial state, was also

experienced as a way of life” (Jayal 2006:37). How adivasi groups define and maintain
their niche as Indian nationals, participate in local and national government, and take part
in the process of planning and implementing necessary health care services within an
established system is something to be further examined.
Development, which could be considered a double edged sword depending on
context, has been studied at length by many (Alliband 1983; Almy 1977; Belshaw 1974;
Cernea 1995; Escobar 1991; Frank 1966; Gow 1993; Hoben 1982; Kottak 1990; Pillsbury
1995; Pinto 2004; Schneider 1975; Yunus 1997), and may be defined as a “far-reaching,
continuous, and positively evaluated change in the totality of human experience” (D.
Harrison, 1988:xiii). Development, which some may view as a form of neo-colonialism,
a way of forcing open the doors of the Third World for the First World to continue to
exert its power, could be interpreted as espousing a secular theory of salvation, the Third
World being perceived as in need of saving for a variety of reasons. Studies of the
“Development of Underdevelopment” reveal a long history of colonial domination in
which Western metropoles siphoned off peripheral resources, a system of dependence
developed in which the colonized country became dependent on the colonizer for
infrastructure and services, and a “metropolis-satellite structure” emerges (Frank 1966).
India has experienced colonial rule and its after-effects on a number of levels,
many of which impact the local political economy and the health care system (Pinto
2004). With colonialism being driven by the industrial revolution, and capitalism being
the driving force behind industrial enterprises, “underdeveloped” countries such as India
were diamonds in the rough, representing places or people to be developed, and thus

made into something more than they were. Development projects sponsored by foreign
entities were believed by some to be a viable option that could benefit many countries.
Frank (1966), who is credited with initiating the examination of the “development of
under development” notes how colonialism has resulted in vast development initiatives
with numerous benefits for the colonizer and devastating “underdevelopment” of the
colonized nation through the loss of power, resources, and autonomy.
The losses experienced by the colonized people are vast, creating a system of
stratification, separation, and extreme power differential. Power differential, which is at
the base of colonial relationships, creates a severe dichotomy that lingers after the
colonial relationship ends. Such may be the case in India, where different groups
receive differing levels of health care, possibly as a result of their former colonial status
(W. Ernst 2007). The scope of most health care services available and/or accessible to
Indian adivasi at times is difficult to accept when we consider that “among the great
achievements of humankind in the twentieth century have been the enormous
improvements in health worldwide” (Findley 1992a:ix). Unfortunately, the “enormous
improvements” in health care noted above by Findley have not yet completely
permeated all regions of the world.
The evolution of biomedicine in India is disputed. Worsley states that Western
medicine “had spread via the Arabs, to India, by around 750 AD” (Worsley 1982:317),
while Nagla credits the British with the introduction of allopathic medicine to India
(Nagla 1997:121). Kumar notes that medical science “was introduced from the top by the
colonial government on and above the traditional medical sciences” whereby they

“trimmed, shaped and conducted the growth of Western medical science to attend,
promptly and appropriately, to the callings of the Empire” (A. Kumar 1998:17). The
establishment of the Indian Medical Service (IMS) was an effort to regulate the provision
of medical services and to keep Indian nationals who practiced biomedicine in a
subordinated position to the Anglos.
Kadipani and Kawant both have had Indian government-sponsored health care
interventions, all offered free of charge to recipients, and aimed at exerting a direct
impact on some aspect of adivasi quality of life, be it the reduction or elimination of
certain diseases, or the control of fertility. For example, toward the end of my fieldwork,
local health care workers told me of a polio vaccine program that was to be rolled out
soon. They invited me to accompany them, but the start for the program was after my
return home date. While at the government hospital in Kawant, I observed a family
planning “camp” being held. Adivasi women sat lined up along a wall waiting for their
turns to speak with the surgeon about tubal ligation. Since both health status and family
size may impact individual and local economies, it follows that examining this
phenomenon would be beneficial.
Ethnomedical and Biomedical Health Care Practices
India is a country of approximately 1.12 billion people (United States Central
Intelligence Agency [CIA] 2007) with a history reaching back 5,000 years (Walsh
2006:xiii). Over time, India has developed a number of ethnomedical/indigenous/folk
medicine and scientifically-based healing biomedical/allopathic methods (Paul 2005),

with some ethnomedical healing practices like Ayurveda and herbalism having been in
place for ages, while other practices, such as biomedicine, being relatively recent.
Ethnomedical health care practices are found in cultures throughout the world.
Considering India, Jaggi notes that “the practice of medicine among tribal people and
villagers today, follows the same pattern it did two thousand years ago” (Jaggi 1973:xiii),
with beliefs persisting that illness is caused by evil spirits, ghosts, malevolent gods,
witchcraft, and sorcery. These beliefs are important to my examination and analysis of
current health care systems in India, especially those accessed by the Rathwa.
Ethnomedicine or ethnomedical health care practices in India include aspects of
indigenous knowledge, indigenous healing, folk medicine, faith healing, or
magicoreligious based practices of healing. Ethnomedical practices and practitioners,
which are available in both Kadipani and Kawant, and are readily accessed by the
Rathwa, may be considered part of a the Rathwa cultural system concerned with sickness
and healing (Hahn 1995:4, emphasis added), or “those beliefs and practices relating to
disease which are the products of indigenous cultural development and are not explicitly
derived from the conceptual framework of modern medicine” (Rubel and Hass
1996:116). Health and well being are not just bodily issues, but also social issues that
have impact at both individual and group levels (Nichter 1992:x)
The impact of a society’s cultural beliefs about health and sickness on individual
and group health status is noteworthy to the planning and provision of health care
services. Equally important is the process individuals or groups go through when making
a health care decision either for themselves or others. Of increasing import is the co-

occurrence of two different health care systems (ethnomedical and biomedical) providing
services for the same patient, which may sometimes be oppositional, and other times
collaborative or complimentary.
During my fieldwork, I could not help but notice the many private clinics in
Kawant, all of which provide health care service for the Rathwa and others. I found this
proliferation of private clinics interesting when I considered that prior research has
indicated that adivasi groups experience varying degrees of health care-related services
(Joshi 2004:403), such as limited availability, poorly trained practitioners, or practitioners
who are self-appointed, lacking the credentials to properly care for the sick and diseased
(Langford 1999).
When I conducted structured interviews with both ethnomedical and biomedical
HCPs, we spoke at length about their medical training, including questions about
education, years practicing, and any areas of specialization. I also asked each HCP to rate
the overall health of the Rathwa, and asked each to explain why he or she deemed the
Rathwas’ health status as a group to be excellent, good, fair, or poor. Commons themes
supporting these categories emerged, with issues of hygiene, overwork, and lack of
knowledge about disease processes being the most common.
Malaria
Malaria has a long history in various parts of the world, most notably Africa, Asia,
South East Asia, and Latin America. With modernization and a change in the
environment, malaria disappeared from some regions, but continued to flourish in others.
Most seriously affected are those living in sub-Saharan Africa, “where stable, endemic

disease is linked to poverty and highly efficient vectors” (Arrow et al., 2004:198).
Malaria is an age-old health problem that continues to plague populations in various parts
of the world today.
Malaria is not a simple disease, nor is eradication easy. Oaks et al. observe “the
nature, duration and severity of malaria infection depend not only on the species of
malaria but also on the level of malaria-specific acquired immunity in the individual”
(Oaks et al. 1993:212). Malaria may have resulted in the deaths of more people than
any other disease (Mascie-Taylor 1993), with infection impacting people’s lives in a
variety of ways beyond the physical or biological. It is a serious threat to not only the
health, but also to the economic and political systems of many communities around the
world, affecting people socially, psychologically, economically, and spiritually (Brown,
1987: 158).
Malaria is endemic to India. In the region where the Rathwa live, Plasmodium
falcipirum, the worst strain of malaria, is prevalent. During monsoon season
(JuneOctober) heavy rains create an ideal environment for mosquitoes to proliferate.
Young children and pregnant women are particularly vulnerable to contracting malaria.
At that time, not only is the habitat ideal for the malaria-transmitting mosquito, but
people are increasingly spending time outside, plowing and planting their fields, and
tending their crops and livestock. The Rathwa pen their livestock in their homes, which
attracts mosquitoes, a practice that has been researched in various sub-Saharan African
countries, and has been determined to put people at risk for increased exposure to the
diseasecausing vector.

Malaria is a vector-borne disease, meaning “diseases which are transmitted by
non-human animals from one human to another” (Heinrich n.d.:28). It is transmitted by
female anopheles mosquitoes during their nightly feeding periods during which time they
bite humans, draw out some of their host’s blood, and deposit a protozoal parasite that
causes severe illness. Malaria is caused by protozoa of the genus Plasmodium, with “four
species, P. malariae, P. vivax, P. falcipuram and P. ovale that parasitize humans” (Mascie-
Taylor 1993:30).
Symptoms of malaria infection are characterized by “fever, sometimes recurring
every second or third day, anemia, splenomegaly, headaches, and a wide variety of other
symptoms” (Mascie-Taylor 1993:30). Malaria infection not only makes some people
very sick, it can also “debilitate victims who eventually succumb to other infections . . .
and suppress fertility, primarily due to spontaneous abortions and premature deliveries
triggered by the malarial fevers and chills” (Brown 1987:158). Without treatment, the
disease may last between 18 to 24 months, with periods of acute illness interspersed with
lapses in symptomology. Repeated infection throughout the year in a locale that
experiences endemic malaria may result in the development of immunity, though
“acquired immunity appears to be relatively short-lived and depends on repeated
exposure to the parasite over time” (Oaks et al. 1991:213).
Malaria is a disease for which there are ethnomedical as well as biomedical
treatments. One ethnomedical treatment used by the Rathwa is neem (Azadirachta
indica), a tree indigenous throughout most of India, and is found in both Kadipani and
Kawant. It is frequently used by the Rathwa both to prevent and treat malaria. Neem has

been noted to be “one of the few drugs that has been extensively studied as to their
pharmacological and clinical properties” (Sivarajan and Balachandran 1994:325), and has
been found to have an antipyretic (fever reducing) effect. Beckerleg, who has worked
with tribal groups in Kenya on ethnomedical practices, notes that neem leaves “are used
for cooling in cases of fever . . . as a palliative for malaria (Beckerleg 1994:312). Tribal
and non-tribal groups alike may self treat malaria symptoms with neem, or use it in
conjunction with biomedical pharmaceuticals (Etkin and Ross 1992). In addition, a
developed resistance to anti-malarial drugs has led to an increase in illness among
vulnerable populations, leaving fewer options for preventing and treating the disease.
Sickle Cell Disease
Sickle cell disease (SCD) is an autosomal recessive blood disorder caused by a
mutation in the gene for the beta-subunit of hemoglobin (Davidson et al. 2000, 588). A
diagnosis of SCD may include individuals with sickle cell anemia, sickle cell
hemoglobin C disease, and the sickle cell beta thalassemias (Platt et al. 1994:1639).
SCD “includes a variety of pathological conditions resulting from the inheritance of the
HbS gene either homozygously or as a compound heterozygote with other interacting
abnormal haemoglobin genes” (Serjeant and Serjeant 2001:23). Outside of India, SCD is
typically found among those of African descent in populations where malaria is endemic.
Serjeant and Serjeant, writing on the “origin of the sickle cell gene” note that “there is
now substantial evidence that the sickle cell mutation has occurred as several independent
events” (Serjeant and Serjeant 2001:17). Their discussion of the “single mutation theory”

postulates that the sickle cell gene was carried to India by migratory peoples from the
Arabian Peninsula (Serjeant and Serjeant 2001:17).
SCD is a disorder that runs in families, the result of a genetic adaptation that
affects hemoglobin, or red blood cells, which carry oxygen throughout the body. Normal
hemoglobin is referred to as type A, sickle hemoglobin is type S. Hemoglobin S “is
produced by a mutated gene coding for one of the blood proteins” (Olney 2000:431).
According to Serjeant and Serjeant,
The inheritance of sickle cell disease obeys the principle of Mendelian
inheritance. When one parent is heterozygous for the sickle cell gene and the
other parent is normal, the offspring would have an equal chance of having either
the sickle cell trait or a normal AA genotype. If both parents have the sickle cell
trait, there is a 1 in 2 chance of offspring having the sickle cell trait, and a 1 in 4
chance of the offspring being normal (AA) or having SS disease. (Serjeant and
Serjeant 2001:33)
SCD is transmitted from one generation to the next when both parents (heterozygous, or
carriers of sickle cell trait) each pass the sickle cell gene to their unborn child. Two
parents with sickle cell trait have a 25 percent chance of having a child with sickle cell
disease. To have SCD, one must be homozygous for sickle hemoglobin. According to
the Sickle Cell Disease Association of America,
Sickle cell disease is an inherited blood disorder that affects red blood cells.
People with sickle cell disease have red blood cells that contain mostly
hemoglobin* S, an abnormal type of hemoglobin. Sometimes these red blood
cells become sickle-shaped (crescent shaped) and have difficulty passing through
small blood vessels. When sickle-shaped cells block small blood vessels, less
blood can reach that part of the body. Tissue that does not receive a normal blood
flow eventually becomes damaged. This is what causes the complications of
sickle cell disease. There is currently no universal cure for sickle cell disease.
(Sickle Cell Disease Association of America [SCDAA] 2009)

Normal red blood cells (RBCs) are shaped like doughnuts, sickle red blood cells
are sickle-shaped (Figure 5). This distortion makes it difficult for RBCs to move through
small blood vessels, causing pain and tissue damage.
Figure 5. Sickle-shaped red blood cells (Holy Cross Hospital 2009).
SCD may be detected as early as 3 months of age or may remain asymptomatic
until adulthood (R. K. Kar 1993). According to Serjeant and Serjeant, the “diagnosis of
the major genotypes sickle cell disease is relatively simple” and includes the sickle test
or the solubility test (Serjeant and Serjeant 2001:41). SCD is estimated to be present in
up to 20 percent of adivasi populations (Balgir 2006; S. Basu 1992; B. C. Kar 1991;
Penchaszadeh 2000), possibly 20 to 30 percent of Rathwa (Dr. Vijay Shah, personal
communication, 2007). SCD, which has been studied extensively in sub-Saharan Africa

populations, is believed to provide some level of protection against an individual
contracting certain types of malaria (Allison, 1954).
The disease itself causes health problems that must also be treated, such as the
periodic manifestation of symptoms associated with sickle cell crisis (SCC). During
SCC, the sickling of RBCs impedes blood flow, which is very painful, and may have
lasting after affects such as: strokes, increased infections, leg ulcers, bone damage,
yellow eyes or jaundice, early gallstones, lung blockage, kidney damage and loss of body
water in urine, painful erections in men (priapism), blood blockage in the spleen or liver
(sequestration), eye damage, low red blood cell counts (anemia), and delayed growth (B.
C. Kar 2002; Sickle Cell Information Center, 2009).
Why Study Malaria and Sickle Cell Disease?
Malaria has a history of ravaging populations, specifically adivasi groups, for
many generations throughout various parts of the world, including parts of India. In spite
of considerable clinical research and the development and implementation of intervention
programs, malaria persists today. Economist Jeffrey Sachs has devoted considerable time
and effort to examining the ramifications of malarial infection on individual, local, and
national economies, as well as how this disease affects the overall health of individuals
and families, especially the most impoverished populations of the world (Malaney et al.
2004; Sachs 2007; Sachs and Malaney 2002).
Sachs proposes that a small amount of money coupled with basic interventions,
such as the distribution of long-lasting insecticidal bednets (LLINs) or the use of
Artemisinin-based medications used in combination with traditional anti-malarials, would

ameliorate the problem, if only large governmental entities would step up to the task
(Finkel 2007; Malaney et al. 2004; Sachs 2007; Sachs and Malaney 2002). Focusing on
the economic and social burden of malaria, Sachs and Malaney observe that “long before
economists attempted to estimate the costs of malaria, natural selection had already
demonstrated the phenomenal burden of the disease” (Sachs and Malaney 2002:680).
When health issues are coupled with personal financial issues, a serious problem arises
that reaches beyond the family or household unit into the local community and beyond.
The threat of malaria infection threatens industry, tourism, migration, and over-all
population health status. Such a long-standing problem is well suited to study and
examination by applied anthropologists.
Prior Research
Prior research indicates there is a pressing need for anthropological research that
focuses on the intersection of ethnomedicine and biomedicine within Indian adivasi
culture (Basavanagouda 2004; S. Basu 1992, 1996; R. K. Kar 1993; Lamba and Mehta
1995; Nayak and Babu 2003, Tyagi 2002). Especially, we need to know how this
intersection relates to individual decision making about health care services, the medical
training and competence of indigenous/traditional healers, as well as collaboration
between ethnomedical and biomedical practitioners, in order to develop health care
services that promote and support healthy, sustainable communities (S. K. Basu 1994a;
Joshi 2004; R. K. Kar 1993, 2004; Lamba & Mehta 1995; Nayak & Babu 2004; Thakur

2002). Stratification may occur within a population based on race, ethnicity, gender, age,
religious affiliation, and education level. These variables influence to varying degrees
who gets what type of health care, when, and why.
A number of studies have been conducted in Indian villages regarding villager
perceptions of disease and illness, allopathic and traditional methods of healing, and the
decision-making process. Bhardwaj, who conducted research pertaining to medical
practices, systems of medicine, and villager treatment preferences in four villages in the
Punjab found that “angrezi (English) medicine and allopathic physicians were generally
preferred of the desi (indigenous) medicine and its practitioners, by all the caste groups”
(Bhardwaj 1975:604). Indigenous knowledge, which may include information about the
application of traditional healing methods such as the use of medicinal plants to effect
healing or prevent disease, plays a central role in any examination of a culture’s
ethnomedical practices. Srinivasan (1984) found similar results when conducting
research in villages in Tamil Nadu. Villagers had a greater faith in allopathic medicine
and were more open to receiving treatment from allopathic physicians, including services
such as immunizations for children (Srinivasan 1984).
Pinto, who has conducted fieldwork in the Sitapur district of Uttar Pradesh in
North India, writes “in much of rural North India, government and nongovernment health
institutions are part of the fabric of everyday life” (Pinto 2004:337). These institutions
may include the sacred and secular, such as shamanism and ritual curing (Kleinman
1980), faith healers, midwives, herbalists (Joshi 2004) or persons of “self-made medical
authority” (Pinto 2004:337). Langford (2002), who has researched trends in Ayurvedic

medicine practices in India, has discovered a tendency for there to be blending of
ethnomedical and biomedical practices by one practitioner, with very little formal
justification, other than a notion that if the combination makes the patient better, no harm
is done.
Thus, my research examines an issue that has been well documented. Medical
anthropologists such as Dressler et al. (2005), Garro (1998a, 1998b, 2000), J. C. Young
and Garro (1982), Nichter (1992), Nichter and Nichter (1989, 1996), and Nichter and Van
Sicklen (2002) have explored why people in various cultures make certain health care
decisions, such as choosing an indigenous healer for some types of illnesses, and an
allopathic or biomedical practitioner for others. The populations these researchers have
worked with live in various parts of the world, with differing belief systems and cultural
practices related to sickness and health, healing and health care, but they are all seeking
ways to ameliorate suffering due to sickness or disease.
Summary
The Rathwa face a variety of health-related issues, many of which have major
impacts on their quality of life, including malaria and sickle cell disease. The HCPs I
interviewed spoke of difficulties those with SDC experience during SCC, which is
brought on by factors such as stress or extremes of temperature. While the HCPs
provided me with a very long list of Rathwa health-related issues I could study during my
time in the field, I decided to focus on malaria and sickle cell disease for a variety of
reasons.

I had a number of questions related to my research questions that I wanted to
answer. First, I wanted to know what the Rathwa knew about malaria, and their
approaches to preventing and treating the disease. I also wanted to determine their level
of knowledge of SCD, such as its causes, symptoms, and treatments. Recognizing that
people anywhere are going to do tomorrow what they do today unless there is a
compelling reason not to, my goal was to determine to what extent socially constructed
beliefs influenced their treatment of not just malaria and SCD, but other illnesses as well.
I wanted to know if health care-related decision making differed by patient age, gender, or
some other factor, such as being the primary wage earner in the household. I was curious if
patient gender influenced what type of HCP one sought treatment from, and the degree to
which spiritual practices were utilized to prevent or treat illnesses.
I also wanted to examine the economic side of sickness, specifically malaria.
Jeffrey Sachs has written in detail about the economic impact of malaria on local
communities as well as entire industries and countries, though primarily in Africa. I
wanted to see first hand what it was like to live in a community where malaria was
endemic, where economic development programs were underway, and where the people
had a variety of approaches to preventing and treating malaria.
I was also interested in the impact of modernization, or modernity, on traditional
health care and healing practice among the Rathwa. India has a long history of
ethnomedical practice, the most well know being Ayurveda. The Indian government has
been promoting Western/allopathic/biomedical health care practices, in some instances as
a replacement for traditional methods of healing. From my preliminary visit, I knew that

some Rathwa sought the services of faith healers called bhouas, and that the bhouas were
one health care treatment option among several that someone could choose when the need
arose. I wanted to determine how Rathwa perceptions of the bhouas might be changing
in response to an increase in availability of non-faith based health care options, such as
allopathy. Was the status of this tradition changing, and if so, why and how?
I could have studied populations dealing with malaria and SCD in many African
countries, a continent where these two diseases have been extensively researched by
people in a wide variety of disciplines. Working with the Rathwa, I had the opportunity
to make a contribution to the research and literature on both the medical and economic
aspects of malaria and SCD outside of Africa, thereby expanding the knowledge base on
how different cultural groups approach these two diseases.
The long-standing history of ethnomedical health care practices in India in
general, and among the Rathwa in particular, coupled with the increasing availability of
biomedical health care services provides an ideal environment for examining how these
two distinct health care systems interface. Recognizing that people anywhere are going
to continue to practice what has worked for them in the past unless they have a
compelling reason to do otherwise, it follows that an examination of the confluence of
ethnomedical and biomedical health care practices among the Rathwa would shed some
light on how and why people gravitate away from traditional health care and healing
practices toward newer, more modern health care and healing practices. My intent is to
understand that compelling reason for changes in Rathwa health care practices.
CHAPTER THREE

THEORETICAL FRAMEWORK
Introduction
In this chapter, I offer a critical review of relevant literature, drawing primarily
on scholarship in medical anthropology, as well as a detailed discussion of social
constructivism, political economy, modernization, and feminist theory, showing how
these provide the theoretical frameworks for my research.
Theory and Medical Anthropology
Theories and practices in medical anthropology have evolved in response to the
historical, political, and economic situations of the times (Escobar, 1991:659), reflecting
changing viewpoints and addressing contemporary issues. Morgan laments that “medical
anthropologists have too often overlooked the political and economic determinants of
disease” (Morgan 1987:131), focusing on other aspects, possibly missing critical
revelations due to an overly narrow perspective. Anthropologists have long recognized
that so much of what people can, and actually, do to improve the quality of their lives is
tied to history, money, access, power, information, and culture—factors that change over
time and in response to many things that are frequently beyond their control.
Scholarship on concepts of health care and healing strives to determine why
people think and act as they do when it comes to making health care choices (Garro
2000:319), such as using home remedies, practicing religious ritual to evoke healing, or
seeking the services of ethnomedical or biomedical health care providers. Numerous
researchers have examined the process by which individuals in a wide variety of cultures

make decisions about health care and healing practices, what prompts them to make these
decisions, and the outcomes of their decisions (Abelson and Levi, 1985; Chrisman, 1977;
Garro 1998a, 1998b, 2000; Gladwin 1989; Kayser-Jones 1995; Mathews 1982, 1987,
1990; Mathews and Hill 1990; Weller et al. 1997; J. C. Young and Garro 1982, 1994).
Each researcher has looked at culturally significant factors that guide informant health
care decision making, including those that influence who makes decisions and when, and
the hierarchy of possible options for health care or healing services. From a theoretical
perspective, a researcher may consider the social context within which someone lives,
their culture, and how shared beliefs and practices pertaining to sickness and disease
move people to seek treatment. Within a specific social context, a researcher may also
consider how the economic situation of the community or region, as well as its political
focus, may impact not only the seeking of health care services, but also the way in which
such services are provided.
Using a model or models to develop theory about the phenomenon being observed
is part of the analysis of health care decision making with any population. Since concepts
of health and disease are influenced by cultural values, and tend to be dynamic rather
than static (Loustaunau and Sobo 1997:17), it follows that a theoretical approach to
sickness and health would be responsive to changes within cultural beliefs and practices.
I utilized Nichter’s framework of health care systems (Nichter 1992:x) for my research,
including:
(1) an examination of the continuities and discontinuities of the health care systems the
Rathwa have access to; (2) an examination of Rathwa health care seeking behavior within

their pluralistic health care system as it relates to age, gender, and socioeconomic status;
(3) an examination of how the Rathwa classify illness, specifically looking at their
language of illness and how they conceive of, or conceptualize health, sickness, illness
and disease, and (4) how these concepts of health and sickness influence health care
decision making in general, and in specific how they prevent and treat malaria, as well as
their treatment of sickle cell disease, two serious health concerns the Rathwa frequently
seek treatment for (personal conversation with a group of Kawant ethnomedical and
biomedical private clinic doctors, June 2007).
In determining theoretical approaches to take to my research, I considered my
research questions, the goals I wanted to achieve through my research, and the methods I
would utilize to achieve my research (de Munck and Sobo 1998:260). Developing theory
about a particular phenomenon is a complex activity that requires the researcher to be
cognizant of what is going on within a particular situation, to be able to determine, assess,
and analyze themes or domains that occur and recur within the phenomenon being
observed, and to make theoretical decisions based on the data collected rather than from a
preconceived notion of what or how something should be. I entered the field prepared to
conduct my research from social constructivist and political economist theoretical
perspectives. My goal was to determine how health care decision making was influenced
both by locally held beliefs and practices pertaining to health and illness, as well as by
local and wider economic forces. Once in the field, I noticed gender-based differences in
how health care decisions were made and want to learn more about what factors influence
who gets what type of health care and when.

Social Constructivism
Social constructivism, or the social construction of reality, was introduced by
Peter Berger and Thomas Luckmann in the 1960s. They explain that “reality is socially
constructed . . . a quality appertaining to phenomena that we recognize as having a being
independent of our own volition” (Berger & Luckmann 1966:1). The social construction
of reality is a dialectic whereby humanity creates reality and thereby produces itself
(Berger & Luckmann 1966). Social constructivists “believe that what people know and
believe to be true about how the world is constructed or made up” (LeCompte and
Schensul 1999b:48).
Social constructivism may be defined simply as “the reality we make, not find”
(Pittman 2000:11), more complexly as “structures of human association determined
primarily by shared ideas” (Wendt 1999:1). Social constructivism recognizes that,
“meaningful behavior, or action, is possible only within an intersubjective social context”
(Hopf 1998:173); it considers the “way in which rules and norms condition actors’
selfunderstandings, preferences, and behaviour” (Reus-Smit 2004:3). This is a world
view in which “individuals seek understanding of the world in which they live and work.
They develop subjective meanings of their experiences—meanings directed toward
certain objects or things” (Creswell 2007:20). The world of health care systems is
socially constructed by the people who define the meaning of health, sickness, illness,
and disease, as well forms of treatment.
Hahn notes that “the culture of a society constructs the way societal members
think and feel about sickness and healing” (Hahn 1995:77). The social construction of

the reality of health, sickness, illness, and disease is culturally specific, and is an ongoing
and dynamic process within a culture or specific group, being influenced by a variety of
factors, that may, over time, modify existing socially constructed reality, such as with
exposure to new cultures and beliefs systems, which may occur through the processes of
modernization and globalization, the introduction of new technology, or acculturation.
Socially constructed reality, which is the world view of individuals and the groups they
belong to, is what influences people when they prepare to make, or actually do make,
decisions about health care for themselves or others.
In the case of health care decision making and members of adivasi or non-adivasi
groups, world view, rules, and norms would be culturally-based and specific to those
groups. If the prevailing belief system is that all sickness is caused by evil spirits, or
malevolent beings such as witches, then the primary choice for treatment will be one that
seeks to either appease the spirits or counteract the forces of the witch. Ferguson and
Mansbach observe that,
Constructivists maintain that we as agents act in the world (subjectively) in
accordance with our perceptions of that world, that the world as it is (objectively)
helps to shape (but may not be the same as ) those perceptions, and that both
perceptions and actions in turn have an impact on the objective nature of the
world. (Ferguson and Mansbach 2004:49)
Social constructivism’s utility is attributable to its “insights into the interplay of
institutions, norms and identities” (Acharya 2001:15) in that it emphasizes “the
importance of normative as well as material structures, the role of identity in the
constitution of interests and action, and the mutual constitution of agents and structures”

(Price & Reus-Smit 1998:259). This is significant because “all social communities rely
on norms of behavior” (Acharya 2001:24) which are ingrained within their world view.
Clearly “intersubjective factors, including ideas, culture and identities” (Acharya
2001:27) influence perceptions of health, illness, sickness and disease, as well as how
individuals and groups make decisions about whether to see an ethnomedical or a
biomedical health care practitioner for their health concern, and when to see which type
of practitioner. Do they first go to their local ethnomedical practitioner and, if their
condition does not improve, do they then seek the services of a biomedical practitioner?
Do they access the services of each type of practitioner in tandem or simultaneously,
hoping for, or relying on, the potential for a complementary relationship to take place?
Individual beliefs about health, healing, illness, and sickness are socially constructed
within a specific cultural framework, one which is particular to the society, ethnic, or
religious group one is a member of (Findley 1992b; Hahn 1995; Jaggi 1973; R. K. Kar
1993; Kleinman 1980, 1988; Paul 2005, Thakur 2002; Tyagi 2002). Paul states that
“every culture, irrespective of its simplicity and complexity has its own system of beliefs
and practices concerning health and ill-health and treatment of diseases (Paul 2005:258).
As a socially constructed phenomenon, illness behavior is “strongly influenced by social
expectations and ideas about illness . . . made and experienced differently in different
societies” (Lewis: 1993:94), being shaped and influenced via social experiences and
learning one goes through over a lifetime.
Kleinman, who has conducted extensive research on health, health care, culture,
posits that “health care systems are socially and culturally constructed. They are forms of

social reality” (Kleinman 1980:35). If we understand the social reality of a culture, we
may be better able to understand the social reality of how people in that culture go about
making health care-related decisions. Since reality is socially constructed, it follows that
individual and group beliefs about the origin or causes of health, sickness, illness, and
disease, as well as beliefs about systems of health and healing are also socially
constructed within a specific cultural framework.
The social construction of disease and illness may fall into two different
categories, naturalistic and personalistic. In naturalistic systems “illness is explained in
‘impersonal, systematic terms’ with disease resulting from ‘such natural forces or
conditions as cold, heat, dampness, and above all, by an upset in the balance of basic
body elements” (Garro 2000:307). Personalistic systems, which differ from naturalistic
systems, focus on the explanation of misfortune, which is believed to be caused by some
outside force, such as a witch of sorcerer, evil spirit, or deity (Garro 2000:307). When
faced with sickness, individual’s socially constructed beliefs tied to that particular illness
guide their decisions as to whether they should wait out the sickness (hoping it will
resolve itself), treat it with home remedies, or seek the services of either an
ethnomedical or biomedical health care practitioner.
Dressler and colleagues have used a social-constructivist model to examine health
disparities, race and ethnicity in a community in the United States (Dressler et al. 2005).
They discovered that the social-constructivist model “offers greatest promise to explain
disparities” in health care when compared with a racial-genetic model, a health-behavior
model, a socioeconomic status model, and a psychosocial stress model (Dressler et al.

2005:). The social-constructivist model “takes into account the dual nature of human
existence . . . what is taken to be the reality of life is in large part a cognitive
representation, constructed out of an amalgam of socially shared understandings”
(Dressler et al. 2005:241). It is these socially shared understandings that shape
perceptions about health and illness within a group or society.
Garro (1998a, 1998b, 2000) has also applied the social constructivist model to her
research on health care decision making with two very different groups, the first in
Pichataro, a community located in west-central Mexico, and the second being the
Anishinaabe in southwestern Manitoba, Canada. Garro found that each group socially
constructed their beliefs around health, sickness and healing. These beliefs influenced
informants’ decision making when seeking treatment for illness, such as in the cases of
“Anishinaabe sickness,” “bad medicine,” or “White man sickness” (Garro 2000). During
her fieldwork with the Anishinaabe, Garro used participant observation, free listing,
interviews and questionnaires to collect data and map the health care decision making
process.
Garro’s findings indicated that the Anishinaabe’s socially constructed beliefs
about certain types of sickness directed their health care decision-making process. This
was the case with “Anishinaabe sickness” which “may be suspected when a physician is
unable to cure an illness or if the illness does not seem to be an ordinary one” (Garro
2000:324). The cause of “Anishinaabe sickness” may be witchcraft or the work of some
malevolent non-human entity.

Alternatively, during her work with the Pichataro community in Mexico, four
treatment options were available (1) home treatments, (2) treatment by folk curers
(curanderas), (3) treatment by practicantes (local unlicensed practitioners of
biomedicine), and treatment by a physician (Garro 2000:310). Using free listing and
questionnaires, Garro found that “according to Pichatarenos, experiencing strong
emotions (such as anger, joy, fright, desire, sorrow, humiliation, and sadness) may lead
to illness” (Garro 2000:314). Her questions to participants about how they respond to
illness were designed to get at the relationship between “cultural knowledge and what
people do when faced with illness” (Garro 2000:315). Garro found that the illness cases
she analyzed “illuminate how illness and care seeking are socially and culturally
embedded” (Garro 2000:330).
Waxler examines the way that individuals diagnosed with Hansen’s disease, or
leprosy, “learn to be lepers” (Waxler 1998:147). Her position is that “social negotiations
turn symptoms into social facts that may have significant consequences for the sick
person” (Waxler 1998:147). Because leprosy is “universally stigmatized, stigma may
function as a sort of social protection device” (Waxler 1998:149) that was used to justify
isolating those afflicted with the disease. A “society’s expectations for lepers, its beliefs
about them, have significant influence on their experiences as sick people” (Waxler
1998:153).
Social constructivism is a beneficial approach to understanding how groups and
individuals create their reality around health, sickness, illness and disease, and how they
translate that reality into decisions about health care and treatment modalities. A “key

feature of constructivism is holism or structuralism, the view that social structures have
effects that cannot be reduced to agents and their interactions” (Wendt 1999:138). This
concept may be successfully applied to the analysis of health care systems, such as
government or private hospitals and clinics, where the system is created within a culture
of health or sickness, which is created within a society.
This theoretical model is beneficial to the study of health care decision making
among the Rathwa. Das has conducted research on disease, illness, and ethnomedical
treatment with the Rathwa in Suskal, Gujarat. His research questions explored issues
such as “how do people distinguish good health from bad health? What causes illness
and how much do they attribute to supernatural reasons for falling sick?” (M. Das 2004:
285). Das found that disease causation among the Rathwas was attributable to both
natural and supernatural means, with most diseases being attributed to supernatural
forces. The Rathwas “believe that Sitala-mata or Devi (Goddess Kali) usually causes
small-pox to express her anger. The other local deity, Tilau Mata, when provoked,
afflicts a person with leprosy (Das 2004:288). The deities must be appeased if the person
is to get well.
Social constructivism is the correct theoretical framework for analyzing the health
and healing practices of the Rathwa for a number of reasons. First, many of their
healthrelated decisions are based on personal and group-held beliefs about sickness and
health, such as illnesses being caused by evil spirits, possession by ghosts, or curses
placed by another individual. Second, Rathwa belief in gods of the Hindu pantheon,
which includes worshiping certain deities, or appeasing them when they have been

slighted or neglected, demonstrates that religious or spiritual beliefs socially construct
their behavior, including when faced with illness. The goal of research from the social
constructivist theoretical framework is to “rely as much as possible on the participants’
view of the situation. Often these subjective meanings are negotiated socially and
historically . . . they are not simply imprinted on individuals” (Creswell 2007:20). My
observation of how Rathwa individuals and families approached a variety of health-
related allowed me to see and better understand how important group-held beliefs and
practices are to their daily lives.
Political Economy
Many researchers across disciplines have examined the impact of political
economy on health and health care (H. Baer 1982; Briggs 2004; Crandon 1986; Morgan
1987; Singer 1992). Political economy theory helps explain stratification of people
within a given population, something that is very significant when considering disease
prevalence and issues such as maternal and child mortality. Political economy theory as
it relates to health and health care services is critical to this research for a number of
reasons, not the least of which is how much impact the political economy of the region
may exert on health status and health care decision making. Hans Baer defines the
political economy of health as “a critical endeavor which attempts to understand
healthrelated issues within the context of the class and imperialist relations inherent in the
capitalist world system” (H. Baer 1982:1). Morgan defines the political economy of
health as a “macroanalytic, critical, and historical perspective for analyzing disease
distribution and health services under a variety of economic systems, with particular

emphasis on the effects of stratified social, political, and economic relations within the
world economic system” (Morgan 1987:132).
While political economy theory dates back to Engels, Marx, and others, in the
field of medical anthropology it has been referred to as the “political economy of
disease,” the political ecology of disease, the study of the “social origins of illness” and
“historical materialist epidemiology” (H. Baer 1982:2). Baer notes that “under
capitalism, functional health is a necessary ingredient at least during periods of prosperity
and expansion for the maintenance of an efficient labor force” (H. Baer 1982:14). In the
case of the Rathwa and their political economy, healthy workers are necessary for
operations at places such as the Gujarat Mineral Development Corporation. GMDC is in
the Rathwa’s backyard, employing and providing health care for Rathwa workers, but
possibly also having a negative impact on workers’ and villagers health.
The political economy theoretical perspective is helpful in considering the social
origins of disease, health, and healing among the Rathwa for a variety of reasons. If
disease, health, and healing are socially-constructed concepts, how might these
constructions be shaped by the political economy at local, state, and national levels? How
might shifts and changes in the political economy result in waves of alterations in belief
systems pertaining to disease causation and healing practices? In addition, I consider
how social constructions of disease interact with concepts of political economy within a
specific community, Kadipani village.
An agrarian people who subsist primarily by farming, the Rathwa have a large
commercial enterprise within the limits of their village—the GMDC mine. Some Rathwa

men are employed by GMDC, and through this employment are exposed to economic and
social forces controlled and dictated by entities beyond village boundaries. GMDC,
which is headquartered in Ahmedabad, operates state-wide in Gujarat, and thus exposes
the Rathwa of Kadipani to outside factors such as the inward migration of people to work
at the mine, housing construction for non-adivasi who work at the mine, and the ebb and
flow of commerce within the mining industry.
Modernization Theory
While adivasi groups in India may continue many of their longstanding life ways,
it appears that with increasing exposure to Western or modern methods of treating illness
and disease, as well as government-sponsored programs aimed at addressing health
problems related to poverty, malnutrition, or poor sanitation, indigenous methods of
healing (ethnomedicine) may not be the first line of defense that it was in the past (Paul
2005; Pinto 2004; Rath 2004; Tyagi 2002). “The decline of the traditional system must
be viewed in a much broader framework; the analysis of the far-reaching impact of the
western technological progress on social structures in the countries of the present day
developing countries” (Nagla 1997:30). With an increased availability of biomedical
health care services in more parts of India, ethnomedical practitioners may be falling out
of favor with adivasi and non-adivasi groups alike as the Indian government implements
biomedically-based programs to ameliorate some common and widely pervasive health
problems.
Definitions of modernism, modernization, or modernity are varied, contested, and
loaded with emotion as well as meaning (Alatas 1972; Attir 1981; Bassand 1981; Deutsch

1961; Harvey 1989; V. P. Singh 1981; Stockman 1981). “In the most general sense, the
term ‘modern’ connotes a sense of belonging to the present and an awareness of a past to
which people can link and at the same time distantiate themselves” (Arce & Long,
2000b:4). Appadurai notes that “the world in which we now live—in which modernity is
decisively at large, irregularly self-conscious, and unevenly experienced—surely does
involve a break with all sorts of pasts” (Appadurai 1996:3).
David Harrison defines modernization as “what is ‘up to date’ in a specific
location at any given time. It is usually the result of a process of ‘Westernization,’
involving economic, political, social and cultural changes which contrast with a previous
‘traditional’ stability (D. Harrison, 1988:xiii). Further, Harrison states “there is no one
modernization theory. Rather, this term is shorthand for a variety of perspectives that
were applied by non-Marxists to the Third World in the 1950s and 1960s” (D. Harrison,
1988:1). If there is no one modernization theory, then the field is somewhat open as to
how medical anthropologists may interpret what modernization, or modernization theory,
means to health care systems, individual and group decisions about health care options,
and the evolving role of ethnomedical and biomedical practitioners.
What is fairly consistent among these definitions of modernization is the
assumption that modernization is a social process, in which one culture or society adopts
the characteristics of another culture or society. Typically, the “giving” culture is more
“advanced” or “developed” in some respect than the “receiving” culture. A typical
example is the perceived influence of countries of the West (America and Europe) on
those of the East (Asia). The introduction of “Western” biomedicine into India has

brought about changes in the provision of health care services throughout the country,
including impacting peoples’ choices about when to access ethnomedical health care
services and when to access biomedical health care services. The “modernization of
Ayurveda, for example, can be considered a process in which modern institutional forms
reshape patients’ and practitioners’ conceptions of the body” (Langford 2002:13).
The rubric used to determine who or what is modern varies. Berman, quoted by
Harvey, states, “To be modern is to find ourselves in an environment that promises
adventure, power, joy, growth, transformation of ourselves and the world—and at the
same time, that threatens to destroy everything we have, everything we know, everything
we are” (1989:10). Bassand’s description of modernization speaks volumes. He
remarks, “Modernization—a term loaded with meanings, if ever there was one! It
connotes the multiple, more or less interdependent changes that have over taken
industrial societies . . . a break with tradition or with all known social and cultural forms
of the past” (Bassand, 1981:215). The tensions surrounding the consequences, positive
and negative, of modernization exist not only with local communities undergoing
development but also within the scholarly and activist literature.
Attir and colleagues, writing of “societal modernization,” note that “no consensus
exists as to a definition of modernization;” however, it has certain characteristics such as
socioeconomic development, including “increased literacy, greater industrialization and
urbanization, and higher living standards” (Attir et al. 1981:197). India has experienced a
considerable amount of development since independence. With increased globalization,
there has been a concomitant increase in industrialization, as well as growth in the

technology sector. Deutsch, quoted in Attir et al., defines modernization as “the process
in which major clusters of old social commitments are eroded and broken and people
become available for new patterns of socialization and behavior” (Attir et al. 1981:197).
Appadurai postulates that “the dynamics of global cultural systems as driven by the
relationships among flows of persons, technologies, finance, information, and ideology”
(Appadurai 1996:47) lead to cultural change, what we may refer to as modernization, as
all of these flows are modern phenomena.
Alatas, writing on modernization and social change in South East Asia, notes that
modernization is attributable to “one basic process, the development and application of
modern science” (Alatas, 1972:23). He points to a need to distinguish modernization
from Westernization, observing that though “the basic ingredients of modernization are
derived from the West, nevertheless it is possible to consider them as autonomous
cultural elements which are subject to diffusion without necessarily being accompanied
by Western culture” (Alatas, 1972:24).
Stockman observes that, “nearly all modernization theorists have agreed that the
process of modernization refers to following in the footsteps of societies like those of
the Western world” (Stockman, 1981:233). Western biomedicine has blazed trails in
countries, regions, and locales that in the past have not been exposed to its basic tenets,
resulting in the diffusion of biomedical health care practices accompanied in part by
changes in local systems of belief. Harvey states that “modernism is a troubled and
fluctuating aesthetic response to conditions of modernity produced by a particular
process of modernization” (Harvey, 1989:99), that while beneficial in some situations,

such as the availability of modern medical care and technology, may also lead to the
loss of age-old cultural practices that are significant to the identity of a particular
cultural group.
Bassand outlines specific factors pertaining to the process of modernization.
These include: “Techno-economic modernization,” which pertains to the effect of science
and technology on a country’s economy, and the subsequent changes in its mode of
production; “Political modernization,” which looks at the relationship between the
government and society, specialization, centralization, and democracy; “Cultural
modernization,” a move from traditional to modern, the emergence of the individual, and
a culture’s realization of its place in relation to the rest of the world; and, “Modernization
of time,” which denotes an “end to the cyclical time of traditional societies” (Bassand,
1981:215).
In terms of ethnography and modernity, Appadurai’s theory of “cultural flows”
considers what ethnography needs to look like now, how the politics of ethnography have
changed or are changing, and what concepts that have served anthropology in the past
need to be re-imagined in response to changes in the world. This reflexive process serves
to establish imagination as a social practice that is part of an ethnographer’s work,
creating a new mind space for interpreting culture within a modern world. For
Appadurai, modernity “is at large” (Appadurai 1996:19), a point which speaks to the
constant state of flux within which globality, locality, identity and the nation-state reside.
Appadurai’s five dimensions of global cultural flows: ethnoscapes, mediascapes,
technoscapes, financescapes, and ideoscapes provide a framework for interpreting current

anthropological phenomena within the multiplicity of “imagined worlds” (Appadurai
1996:33). The construction of the imagined worlds of locality and nationalism are
facilitated by one’s exposure to the media, technology, increased mobilization, migration,
transformations in ideology, material culture, representation, identity and globalization.
The ever increasing reach of globalization has “shrunk the distance between elites,
shifted key relationships between producers and consumers, broken many links between
labor and family life, obscured the lines between temporary locales and imaginary
national attachments” (Appadurai 1996:10). We are part of a morphing modern world
that we shape and are shaped by, making us and our culture a product of our own being-
ness, a world or reality in which “the conceptions of the future play a far larger role than
ideas of the past” (Appadurai 1996:145).
Appadurai offers a theoretical perspective on the pre- and post-colonial
experience, as well as identity and modernity. His theory “is not an update of older social
theories of the ruptures of modernization” (Appadurai 1996:9), but rather an examination
of the everyday factors of life, those cultural flows or units of analysis that are created
within the imagination of each of us and interpreted through the lens of our lived
experiences. Central to the theory of Appadurai’s “cultural flows” is the premise that
imagination is driving the creation, processing, and distribution of information as well as
its interpretation, thereby influencing, shaping, and coloring how we see the modern
world and navigate its constructs.
Through the “flows of culture,” we may better comprehend how issues such as
modern ethnic movements, representation, and identity come to be (Appadurai

1996:157). Placing imagination at the center of this process, and viewing space and time
against his “cultural flows” or “scapes,” what results is an understanding of identity that
is molded by what is happening now, more so than what has happened in the past. The
characteristics or factors that people choose as signifiers to identify or define themselves
as individuals, or as part of a group, are as varied as the people and the groups
themselves. These characteristics can be tied to, or indicative of, local, national, regional,
political, ethnic, racial, sex, gender, religious, or other affiliations. What is crucial is that
self and/or group identity speaks in some way to how an individual or group sees
themselves in their daily lives, as well as a part of their locality, nation, or the world.
Appadurai notes that “conceptions of the future play a far larger role than the
ideas of the past in group politics today” (Appadurai 1996:145). Since “modern
nationalisms involve communities of citizens in the territorially defined nation-state
who share the collective experience” (Appadurai 1996:161), it follows that the local,
neighborhood, and national identities of the Rathwa would be a collection of who is
living in Kadipani, what they are experiencing, and what they are being subjected to
via cultural flows such as ethnoscapes, ideoscapes, technoscapes, mediascapes, or
financescapes. These self and group generated “scapes” exert an influence that may
be subtle and diffuse, a normal part of the mundane world, comprised of hard and soft
cultural traits that result in a gradual transformation or revised definition of the local or
national imagined world and reality. Each of Appadurai’s “scapes” contributes to the
interpretation of modernity—what is it, where it came from, how it got here, and
where it is going.

Appadurai’s theory on the production of locality and neighborhood involves a
degree of internal colonization, an experience in which what is turns into what will be,
while what will be is influencing what is. This position is one of introverted contextual
influence and analysis, a circular model for explaining how identities are created on
various levels, which then in turn influence changes on multiple levels. He draws from
the context within which change evolves, as well as considering how the evolution
creates context itself. For the Rathwa, one way to maintain their identity as an adivasi
group is to preserve certain cultural beliefs and practices that distinguish them from other
adivasi groups.
In the case of health care in India, the increasingly rapid diffusion of scientific
approaches to diagnosis and treatments, as well as increasingly available technology,
have led to situations where, via various forms of technology such as computers, doctors
may perform virtual examinations of patients who may be hundreds of miles away. Even
with these advances in technology, Baer notes that “more people in the underdeveloped
capitalist nations seek the assistance of traditional or folk healers than that of the agencies
of cosmopolitan medicine” (H. Baer 1982:15). This appears to be the case with the
Rathwa, some of whom hold fast to their traditional healing and health care practices,
including the use of faith healers and home remedies prepared from locally-grown
medicinal plants.
Modernization is a viable theoretical approach for explaining the evolution of
health care systems in India today, or any country for that matter. The mere increase in
available technology such as cellular mobile phones and computers has greatly impacted

to delivery of health care, as well as the choices people have for health care services.
Ever increasing globalization, especially in India where the technology sector is
expanding, has resulted in cultural changes across the board, not just in the health care
arena.
Feminist Theory, Adivasi Women, and Health Care
Much has been written across disciplines on health status as it relates to gender,
specifically that of females (Barroso, 1994; Candib 1994; Dan 1994; Hamilton 1994; M.
Harrison, 1994; Himmelgreen et al. 1991; Lorber 1997; Lupton 1994). Lupton (1994)
notes the various “waves” within the feminist movement and feminist theory as they
relate to the evolution of how women, health, and biomedicine have been conceptualized
over time. Biomedical and non-biomedical concepts of the female body, its ability to
reproduce, the power behind this, as well as the limitations imposed by it, have been
critical to developing an understanding of placement of women within the context of
biomedicine, health care, and reproductive technologies.
Lupton (1994) takes a political economy perspective of women and power, within
the framework of the woman as patient and health care recipient and the doctor as health
care provider. I was curious as to what power Rathwa women have over their own bodies
in relation to issues such as contraception, childbirth, health care in general, and their role
in the health care decision making process for themselves and their family members.
Feminist theory may help explain who receives what type of health care and
when, as gender is a significant factor in Indian culture. Concepts of the female body, the
view of women as those responsible for reproduction, as well as the perceived power

behind this, or the limitations imposed by it, have been critical to developing an
understanding of placement of women within ethnomedical and biomedical healing and
health care practices. Lupton writes of the political economy perspective of women and
power within the framework of the woman as patient and health care recipient and the
doctor as health care provider (Lupton 1994:107).
My interest lies with what perceived or real power Rathwa women may have over
their own bodies, as well as those of their family members, when, as the primary keeper
of the home and family, they are faced with having to seek health care for themselves or
someone else. Beyond health and home, Indian women’s role in development is also
critical to this examination and analysis as this project is framed within the local political
economy. Kabeer notes that “one way of charting the emergence of women as a
distinctive category in development discourse is to monitor their changing significance
within the policy declaration and institutional structures of the major development
agencies” (Kabeer 1994:1). The progression of theories pertaining to women, health, and
development illustrates a shift in the role and place of women.
Feminist theory provides a perspective not found in other theoretical approaches
due to its focus on gender and gender-related issues such as the division of labor in the
home, property ownership, and childrearing responsibilities. While feminism and
feminist theory each have multiple meanings, some of them negative, Moore believes that
“feminist anthropology has the clear potential to speak to fundamental theoretical issues
within the discipline of social anthropology” (H. L. Moore, 1988:196). In the case of this

research, I consider the responsibility of Rathwa women in health care seeking behavior,
as well as health care decision making, within the context of long-defined gender roles.
If Rathwa women take part in health care decision making, or the provision of
health care in the home in the form of home remedies, what perceived responsibility
might they hold for failed health care-related decisions or interventions? If a home-based
cure does not work, is the woman who administered the cure at fault? Conversely, if a
woman took a family member to a particular health care provider and the treatment
administered was unsuccessful, who was perceived by others to be at fault, the woman or
the health care provider?
Summary
Prior research indicates that there is a pressing need for anthropological research
that focuses on the intersection of ethnomedicine and biomedicine within Indian adivasi
culture (Basavanagouda 2004; S. Basu 1992, 1996; R. K. Kar 1993; Lamba and Mehta
1995; Nayak and Babu 2003; Tyagi 2002). Also needed is an examination of how a
pluralistic system of health care that includes ethnomedical as well as biomedical health
care services impacts household health care decision making. Absent from the literature
is sufficient research pertaining to the medical training and competence of those
indigenous or traditional healers who practice folk medicine, as well as evidence of
collaborative efforts between ethnomedical and biomedical practitioners (S. K. Basu
1994a, 1994b; Joshi 2004; R. K. Kar 1993, 2004; Lamba & Mehta 1995; Nayak & Babu
2003; Thakur 2002).

My research examines Rathwa traditional health care practices in the face of
increasing health care-related options. Rathwa health care-related decisions are being
increasingly influenced by outside forces that are impacting what they should do and
when, such as in the case of government-sponsored health care programs. While many
cultural groups have pluralistic health care systems available to them, what is distinct
about the Rathwa is that they are now at a crossroad between tradition and modernity.
Tension appears to be developing between what is traditional and what is modern,
including the role of their bhouas, or faith healers. The bhouas existence depends on
faith, and it appears that peoples’ faith in the faith healers are being shaken. Perceptions
of the bhouas are shifting, as are perceptions of those who seek their services. Are people
considered “country” or “backward” if they do not choose modern health care services
over traditional? How will this questioning impact group identity? Might it be as
Appadurai suggests, that “the world in which we now live . . . surely does involve a
general break with all sorts of pasts” (Appadurai 1996:3)?
CHAPTER FOUR
ETHNOMEDICAL AND BIOMEDICAL HEALTH CARE
AND HEALING SYSTEMS AND PRACTICES IN
KADIPANI AND KAWANT
Introduction
In this chapter ethnomedicine and biomedicine are defined. I discuss the various
ethnomedical and biomedical health care systems and their respective health care

practitioners in India, including an explication of the pluralistic system of health care
services available in Kadipani and Kawant villages.
Ethnomedicine and Biomedicine
Medicine may be defined as “the science of diagnosing, treating, preventing or
alleviating disease and other damage to the body or mind” (Konadu 2007: 77). Current
health care and healing practices in India may be classified as ethnomedicine or
biomedicine. Ethnomedicine consists of health-related beliefs and practices of
indigenous groups. Ethnomedicine may also be referred to as indigenous knowledge,
folk medicine, or “non-Western” medicine (Worsley 1982:315). Biomedicine is the
application of scientific principles to clinical medicine. It is also known as western or
allopathic medicine (Dubos 1977; Hahn 1995; Kleinman 1988).
The continuum of training for health and healing practitioners in India has varied
over time, with many ancient texts outlining approaches for dealing with specific
diseases. Nagla, writing on medical training early in India’s history, states:
The study of medicine was encouraged in ancient India. During those days one
could become a physician by learning one of the following courses: (I) learning theory
and practice of medicine as an apprentice to a teacher by living and working with him in
his house; (ii) joining a Gurukula, a residential school situated in the forests away from
human habitation; (iii) attending classes at higher training institutes such as Taxila, Kashi
or Nalanda. (Nagla 1997:25) It is possible to find a combination of ethnomedical and
biomedical health care systems in full force in many countries throughout the world,
many of which manage to successfully respect and complement each other in their care
and treatment of patients (Desai 1980; Kleinman 1980; Worsley 1982). India and China

both have longstanding histories of healing practices from ancient times. In India it is
Ayurveda; for China it is Traditional Chinese Medicine (TCM).
Every culture “has an ideology or fundamental framework used to interpret and
respond to the historical, socio-political, cosmic, and temporal environment (Konadu
2007:19). Since “the understanding of sickness and the response to sickness through
healing vary greatly from time to time and place to place,” and is “fundamentally shaped
by historical and cultural circumstances” (Hahn 1995:1), it is imperative to the
examination of health care practices that time and place be an integral part of the
analysis. Recognizing that the “evolution of medicine is a long story, stretching from
prehistoric to modern times” (U. P. Sinha 1994:151), and that it encompasses many
different treatment modalities that have been richly documented, it is logical that the
examination of any society’s beliefs about health care and healing would include an
analysis of all those systems that directly impact the health status of the population.
Anthropological surveys of healing and health care practices and systems reveal
that “since antiquity, humans had some rudimentary systems of medicine to ameliorate
physical sufferings and disease, in order to lead a productive socio-economic life” (R. K.
Kar 1993:158), and that a wide variety of methods for addressing health issues have
developed over time. Healing and health care practices have evolved and developed over
time in response to scientific discoveries, technological developments, and cultural
change.
Medicine “besides being a process of cure is also concerned with the patient’s
culture, his personality, his norms and values (Nagla 1997:93). Addressing and “treating

bodily ills takes place, in any culture, within a ‘metamedical’ framework of thought”
(Worsley 1982:315), which varies worldwide and is subject to interpretation based on
cultural beliefs and practices within a specific society. Most importantly, the “ways in
which we perceive and interpret health and illness, and seek and deliver care, are
inextricably bound up with cultural norms, beliefs, and values, as well as with social
structure and environmental conditions” (Loustaunau and Sobo 1997:1). In India, as
elsewhere, there may be multiple treatment approaches for any one sickness or disease;
how a health care recipient or other health care decision maker arrives at a choice of
treatment, or a combination of treatments, is culturally-based, and tied to local beliefs
about health, healing and sickness (Basavanagouda 2004; S. Basu 1992; Langford 1999;
Nayak and Babu 2003; Tyagi 2002).
Health, Sickness, Illness, and Disease
Every culture, “irrespective of its simplicity and/or complexity has its own notion
regarding health and health seeking behaviour” (R. K. Kar 1993:158). Hahn posits, “if
the meaning of ‘sickness’ varies widely from one cultural setting to another, what then,
do cultures have in common that might be called ‘sickness?’” (Hahn 1995:5). Is it the
way those that are sick behave, or how they are treated by others? Is it the community’s
response to sickness? Is it how sickness or disease is treated? Or is it the process an
individual or group goes through when deciding how to treat a specific sickness or
disease?
Sickness, or illness, “refers to how the sick person and the members of the family
or wider social network perceive, live with, and respond to symptoms and disability”

(Kleinman 1988:3). Sickness, which is a very personal phenomenon when it happens to
someone, may also be a group phenomenon because the beliefs surrounding a particular
sickness are typically formed within a specific cultural group. According to Harwood,
People who have been raised in an ethnic collectivity—that is, a group with
common origins, a sense of identity, and shared standards for behavior—often
acquire from that experience not only basic concepts and attitudes toward health
and illness but also fundamental styles of interpersonal behavior and concerns
about the world. (Harwood 1981:1)
Hahn defines sickness as “an unwanted condition in one’s person or self—one’s mind,
body, soul, or connection to the world. What counts as ‘sickness’ is thus determined by
the perception and experience of its bearer, the patient” (Hahn 1995:5).
Disease differs from illness in that disease is a biomedical phenomenon, the
“kinds of disorder distinguished on the basis of biological facts, with physiological,
psychological, and anatomical criteria of abnormality” (Lewis 1993:99). Illness pertains
to “those corresponding changes of body or mind that people choose to identify as
undesired and abnormal, the experience and meaning of perceived disease” (Lewis 1993:
99). Disease may imply “submission to the official medical system designed to address
it” (Loustaunau and Sobo 1997:130). Healing may be easier to define in that it is simply
“the redress of sickness” (Hahn 1995:7).
Health is defined by the World Health Organization as “a state of complete
physical, mental and social well-being and not merely the absence of disease or
infirmity” (WHO 2007). This definition, which was adopted April 7, 1948, has not been
modified since. Lieban defines health and disease as “measures of the effectiveness with

which human groups, combining biological and cultural resources, adapt to their
environments” (Lieban 1977:13). Dubos notes the difficulty inherent in defining disease,
but settles on the implication that disease is “any state, organic or psychic, real or
imaginary, that disturbs a person’s sense of well-being” (Dubos 1977:32).
Since the “antiquity of disease is established beyond dispute,” it follows that “a
parallel, ancient emergence of healers, the unique individuals to whom their compatriots
turned for assistance and direction when serious illness or dysfunction disrupted the
ordinary course of life” would also emerge (Wood 1979:291).
A key point when studying individual or group decision making processes
pertaining to healing and health care is that “the societal belief in a certain therapy, be it
indigenous, traditional or cosmic contributes substantially in his recovery” (Nagla 1997:
93). This factor may greatly influence which health care practitioner, be it ethnomedical
or biomedical, is accessed first, which is accessed last, and who receives what treatment
when (e.g., sick male wage earner before sick non-working female or child).
Medical Practices in India
In India “there is an immense heterogeneity of medical beliefs and practices all
over the country” (Paul 2005:259), with adivasi and non-adivasi groups alike having
access to ethnomedical practitioners such as shamans, priests, herbalists, and untrained,
self-appointed healers, as well as biomedical practitioners whose approach to healing is
scientifically-based, and typically backed or supported by the government. Health “to a
tribal community by and large, is a function of the interaction between socio-cultural and

socio-biological practices, the genetic attributes and environmental condition” (Paul
2005:258). Importantly, there are “many tribal health practices, which are highly
beneficial and which can revolutionize treatment processes, even modern medicine”
(Nayak and Babu 2003:308).
Joshi, writing on health care systems in India, notes that “the tribal areas in
general are marked by poor coverage in health care” (Joshi 2004:403) with
inconsistencies in service such as limited availability, poorly trained practitioners, or
practitioners who are self appointed, lacking the credentials to properly care for the
sick and diseased (Langford 1999). Many adivasi communities are “facing extinction
due to endemic diseases” (S. Basu 1992:14) which frequently could be prevented.
In “pre-Independent India . . . the dominant system of medicine was the traditional
system which had no preventative characteristics and its effectiveness for controlling
diseases was very slow and inadequate” (Nagla 1997:60) resulting in long standing
practices which to this day do not always adequately meet the health care needs of the
population. S. K. Basu, who writes extensively on adivasi health in India, observes that,
There are more than 400 tribal groups in India who are exposed differently to the
various climatic and environmental stresses/strains and are characterized by their
individual socio-economic, socio-cultural and socio-biological set up. The health
of these tribal groups is as such a function of the interaction between sociocultural
practices, genetic characteristics and the environment conditions. The widely
varying prevalent health practices, use of indigenous herbal drugs, taboos and
superstitions are also responsible for determining the health behaviour and health
status of the tribal groups. (S. K. Basu 1994a: v)
Culturally-related factors such as penning livestock within the home, poor nutrition due
to dietary sanctions, and the belief in supernatural causes of disease, all may result in

sickness and disease, which may in large part be preventable (Basavanagouda 2004:282).
This could be accomplished via the establishment of culturally appropriate and specific
intervention and education programs, and “formulating effective need-based health care
strategies among these vulnerable tribal groups” (S. Basu 1992:15).
India is a country of approximately 1.12 billion people (CIA 2007) with a history
reaching back 5,000 years (Walsh 2006:xiii). Over time, it has developed a number of
indigenous and scientifically-based healing methods, the most notable of which is
Ayurveda. Nagla, writing on the history of medicine in India states,
During the Atharvavedic period . . . there existed two main types of healing art and
its adherents. The first type largely depended on incantations of magical verses and
sacrificial practices to bring about cures; the second type while using magical
formula, depended more on the empirical-rational use of herbal and other
medicaments. (Nagla 1997:23)
Jaggi observes that “the practice of medicine among tribal people and villagers today,
follows the same pattern it did two thousand years ago” (Jaggi 1973:xiii) with beliefs that
illness is caused by evil spirits, ghosts, witchcraft and sorcery. This continuity of belief
over time about health care and healing practices is significant to the examination and
analysis of current health care systems in India.
The World Health Organization “has set the target of Health for All by 2000 AD.
The objective of this global declaration is to lead the world signatories to the road of
progress” (Nagla 1997:7). The Indian government, as “one of the signatories to the 1978
U.N. declaration ‘Health for All by the year 2000 A.D.’” (Tyagi 2002:35) has made an
effort to increase the availability of biomedical health care services to tribal populations

throughout the country (Paul 2005). Tyagi, reflecting on the fact that India is one of the
“signatories to the U.N. Declaration of Health for All,” observes that “this goal is difficult
to achieve unless we do something extraordinary” (Tyagi 2002:35). That “something
extraordinary” could include an examination and analysis of the relationship between
ethnomedical and biomedical health care systems.
The impact of a society’s cultural beliefs about health and sickness, as well as
individual and group decision-making processed, is significant to the planning and
provision of health care services. Of increasing significance is the co-occurrence of two
different health care systems (ethnomedical and biomedical) providing services for the
same patient, which may sometimes be oppositional, and other times collaborative or
complementary.
The year 2000 has passed, as has the WHO’s goal for achieving health for all by
that date. People in many countries, including India, and more specifically adivasi
groups, are still waiting for improvement in the health care they receive (S. Basu 1992,
1996; Kalla and Joshi 2004; Lamba and Mehta 1995; Nayak and Babu 2003; Rath 2004).
The scope of most health care services available and/or accessible to adivasi groups in
India at times is difficult to accept when we consider that “among the great achievements
of humankind in the twentieth century have been the enormous improvements in health
worldwide (Findley 1992a:ix). Unfortunately, the “enormous improvements” in health
care noted above by Findley have not yet permeated all regions of the world.

Five primary systems of health care are prominent in India today, each with its
own particular methods for promoting health or diagnosing and treating sickness, illness,
or disease. Some of these systems of health care are based more on science, others are
focused on indigenous knowledge, faith and/or religious beliefs. These five primary
medical systems include:
1. Indigenous healing, or folk medicine, which is frequently found among
indigenous or adivasi groups, may be referred to as a type of ethnomedicine. 2.
Ayurveda, a holistic system of health and healing that dates back to
ancient India, is also considered a form of ethnomedicine, especially in the United
States.
3. Homeopathy, a system based on the concept of “Similia Simililus Curantur,”
the belief that like cures like, which escapes classification as either
ethnomedicine or biomedicine; might best be classified as “alternative
medicine.”
4. Unani Tibb, an ethnomedical healthcare practice based on a blending of Ionic
(Greek) and Islamic methods of healing.
5. Allopathy, which is scientifically-based biomedicine (Nagla 1997), is also
referred to as conventional medicine Western medicine (Hahn 1995;
Kleinman 1980, 1988; Konadu 2007), “cosmopolitan medicine” (Loustaunau
and Sobo 1997; Rubel and Hass 1996), “clinical medicine” (Loustaunau and
Sobo 1997), or “scientific medicine” (Finkler 1998:118).

Increased health care choices may influence culture change, such as beliefs
about the causes and treatments of illness. In addition, the introduction of various
health care and healing systems may directly impact mortality, disease incidence, and
health policy development (Qadeer and Visvanathan 2004). In India, “the planning and
implementation of effective strategies for redressing the problem of tribal health needs a
critical appraisal from an anthropological perspective” (Nayak and Babu 2003:302),
especially in light of the increased choices in health care systems available and the
emergence of new health-related concerns.
Ethnomedical methods of healing, such as “shamanism, herbology, faith healing
and the relationship between illness and supernatural forces have captured the interest of
ethnologists and the public from anthropology’s earliest days” (Rubel and Hass 1996:
113). Ethnomedicine has been referred to in the literature as indigenous knowledge,
indigenous healing, folk medicine, faith healing, or magico-religious based practices of
healing. Ethnomedicine may be defined as “the part of a society’s cultural system
concerned with sickness and healing (Hahn 1995:4). In 1968, “Hughes applied the term
to ‘those beliefs and practices relating to disease which are the products of indigenous
cultural development and are not explicitly derived from the conceptual framework of
modern medicine’” (Rubel and Hass 1996:116).
Folk medicine, a type of ethnomedicine, is “generally used to designate
healthrelated belief and practices of traditional societies . . . it is from folk, or ‘unofficial’
medicine that many patients derive their attitudes, values, and decisions about medical

care in general” (Loustaunau and Sobo 1997:109). Folk Medicine “is frequently
classified into sacred and secular parts, but this division is often blurred in practice, and
the two usually overlap (Kleinman 1980:59). Jaggi, writing about folk medicine and its
practitioners in India states,
There are several types of people in the village who practice the healing art. They
are grocer-herbalists, priests, exorcists, removers of evil eye, those who make
charms, amulets and talismans, snake-bite curers, boil and wound experts, those
who put slave in the eyes, thornpullers, barber-surgeons and village dias who
deliver babies. (Jaggi 1973:210)
India “is a country rich in indigenous herbal resources and traditionally the vast
population is accustomed to the use of herbal folk medicines” (Shah 1982:294). These
may include plants found locally such as neem (Azadirachta indica) which is known for
its anti-malarial properties (Shah 1982; Sivarajan and Balachandran 1994). Folk
medicine, which “was practiced during the Atharvedic period . . . is still practiced in
contemporary times” (Nagla 1997: 41), by “indigenous practitioners of traditional
medicine” who “tend to emphasize not the universality of their therapies but their cultural
or regional specificity” (Last 1996:377).
The folk sector of the health care system comprises non-professional,
nonbureaucratized “specialists”. . . part-time, non-registered practitioners
functioning within the context of village organization. . . . Their roles are
validated by social recognition and regulated by the community conventions, the
caste and village leadership. (Nagla 1997:41)
The “indigenous form of medicine has endured centuries of tests and experimentation and
does not deserve the scorn and disbelief with which it is greeted in the antiseptic halls of
‘modern, sophisticated and highly sensitive, technologically precise’ therapeutical
overtures” (Lamba and Mehta 1995:4).

Since cultures vary greatly, it is logical that a culture’s healing practices and
beliefs about sickness and health would also vary considerably. Systems of healing
within cultures develop over time and in response to needs exhibited by the population.
The use of local resources such as plants, animals, or minerals for healing purposes is
seen as indigenous knowledge, something developed and refined locally, with many
some practices lasting for many generations. Indigenous knowledges “deal with the
experiential reality of the world. They are forms of knowledge that reflect the
capabilities, priorities, and value systems of local peoples and communities” (Dei et al.
2000:19).
Ayurveda—India’s Ancient Form of Ethnomedicine
Ayurveda “is treated by anthropologists as an indigenous system of medicine that
is deeply ingrained in Indian society” (Langford 2002:53). Ayurveda, a “classical system
of Indian medicine” (Gupta: 1998:158), is “one of the oldest scientific medical systems in
the world” (Nagla 1997:36) extending back to the Vedic ages (1500–800 B.C.) (Sivarajan
and Balachandran 1994). The term Ayurveda, or “life wisdom” (Ninivaggi 2001:xi) is
“composed of two words—‘Ayur’ and ‘Veda’ which put together literally mean ‘Science
of Life’” (Nagla 1997:36). In India, “Ayurvedic medicine has been officially recognized
by the state since 1962” (Worsley 1982: 318), and is widely practiced today, with private
clinics in villages offering treatment for a variety of maladies.
Ayurveda is a “generic” term for Indian traditional medicine which includes the
use of “herbal medicines, minerals, animal products, food, massage, air, water, heat,
earth, surgery, detoxification and tonification to bring about health” (Pole 2006:xix). It

is the “Indian sastra or discipline directly concerned with health and healing” (Fields
2001:36), with prevention of disease being a core belief, as opposed to the treatment of
disease. It is a purpose driven system of medicine that focuses on life principles and
routines that are essential to maintaining good health. Ayurveda may be considered an
ongoing part of a healthy lifestyle, not something that is used only when faced with
sickness.
In the Ayurvedic system of medicine, “nothing in the world is considered to be
separate from anything else. Everything is interconnected” (Pole 2006:17). Ayurveda’s
comprehensive whole-person approach to health and healing creates a partnership
between practitioner and patient, with the patient being actively involved in his or her
treatment, through “intentional and sustained self discipline, perseverance, and taking an
active, personal role in matters of health and overall lifestyle” (Ninivaggi 2001:xv).
Ayurvedic medicine does not just treat illness, but seeks to prevent it. Ayurvedic
medicine is holistic in its approach, taking into consideration the physical, metaphysical,
and spiritual aspects of health and well being. Its teachings include philosophy,
mythology, diet, and yoga, among other things, all aimed at helping patients achieve
balance and wholeness in their lives (Mishra 2004a, 2004b; Ninivaggi 2001; Pole 2006;
Sivarajan and Balachandran 1994).
Ayurveda is based on “four books of knowledge called Vedas: Rigveda. Samveda,
Yjurveda, and Atharveda (4500 to 1600 B.C.)” (Mishra 2004a:17). Information
pertaining to health and well being was complied and distilled into three books referred to

as “the senior triad (vriddha traya): Charak Samhita, Sushrut Samhita, and Ashtang
Hridaya Samhita” which provide information and guidance issues related to health,
disease, material medica, pharmacology, and much more, all aimed at enhancing life
through health and hygiene (Mishra 2004a:17).
There are eight branches to Ayurvedic Medicine:
1. Internal medicine, including physiology and pathology (Kaya-cikitsa).
2. General surgery (Salyapahartrka).
3. Eye, ear, nose, and throat disease (Salakya).
4. Pediatrics, including obstetrics and embryology (Kaumara bhryta).
5. Psychology/psychiatry: psychotherapy, dream analysis, demonology
(Bhutavidya).
6. Toxicology (visagara-vairodhika-prasamana).
7. Geriatrics and rejuvenation therapy (Rasayana).
8. Sexology (Vajikarana). (Fields 2001:37)
According to Ayurveda, “good health is based on the equilibrium of dosha (humor), agni
(digestive fire), dhatu (seven body tissues), and mala (waste products)” (Mishra
2004b:1). Dosa “is the Ayurvedic term that generally describes our inherited traits,
individual characteristics and tendencies” (Pole 2006:20). There are three dosas: vata
(principle of propulsion), pitta (principle of transformation), and kapha (principle of
consolidation). The dosas are used to describe a person’s bodily constitution. When
there is an accumulation of a particular dosa, ill health results. The goal of Ayurvedic
medicine is to bring balance back into the body.
Historically, the Ayurvedic system of medicine “along with its teaching and
practice remained in low key sometime between 1200-1800 A.D. when the Muslims
entered India as conquerors” (Nagla 1997:26), resulting in an increase in medical

practices based on Muslim belief systems. Langford (1988, 1995, 1999, 2002, 2003),
who has conducted extensive research on the practice of Ayurvedic medicine in India,
today tells of a brief period during which Ayurveda was sponsored by the British
government during colonization, that was then followed by a surge of European-based
biomedicine and a suppression of the practice.
As a long standing, culturally-based practice of healing, Ayurveda has
experienced resurgence, and established a strong hold in the continuum of health care
practices available to adivasi and non-adivasi groups in India today. Over time, Ayurveda
became more prominent, especially of late, and is quite possibly the best known
ethnomedical system of health care practiced in India today. Langford notes that
“researchers have often suggested that Ayurveda has persisted, despite the enormous
competition from biomedicine, precisely because it encodes deep-seated cultural
experiences and values that extend beyond medical diagnosis and cure” (Langford
2002:53). Currently, Ayurveda it is one of four main systems of health care available
throughout India, available to adivasi and non-adivasi groups alike.
Homeopathy: An Imported Form of Ethnomedicine
Homeopathic medicine was developed by German physician Dr. Samuel
Haheneman (1755-1843) during the 18th century. Haheneman believed that “remedies
which, in large doses, could create a particular set of symptoms, could in minute doses
. . . relieve those same symptoms” (Cummings and Ullman 1984:ix). Haheneman,
while experimenting on himself with quinine, a malaria treatment, discovered that he

experienced symptoms similar to those of patients with malaria (E. Ernst and Hahn
1998:ix).
From this experimentation and additional trials, Haheneman claimed confirmation
of his hypothesis that like cures like. He went on to develop methods for preparing
homeopathic remedies for a variety of maladies. These methods involved the dilution of
remedies to the point of barely being able to discern the presence of the remedy in a
solution that had been diluted many times and shaken vigorously. The combination of
diluting and shaking a remedy is what made it a viable treatment.
The word homeopathy is “derived from the Greek words ‘homoios’ meaning like
or similar and ‘pathos’ meaning suffering.” The primary principle of homeopathy, the
Natural Law of Cure, states “like cures like (Similia Simililus, Curantur)” (Nagla
1997:48). The American Institute of Homeopathy Standards of Practice defines
homeopathy or homeotherapeutics as,
A unique scientific system of medicine predicated on the Law of Similars,
“Similia Similibus Curentur,” or, “let likes be cured by likes.” Although this
principle was first postulated by Hippocrates, it had its first practical application
in 1796 when Samuel Hahnemann established Homeopathy. (American Institute
of Homeopathy [AIH] 2007)
Homeopaths “view the body as sustained by a vital energy. The task of the homeopath is
to stimulate this vital force and allow healing to take place” (Furnham 1998:191), “based
on the principle that the best therapy for any given patient is a single medicine whose
adverse effects closely mimic the symptoms of the illness” (Skinner 2001:9). The
homeopath’s role in the healing process is to be “cognizant of the total or holistic nature

of physiological disorder or disease and the necessity of a holistic approach to diagnosis
and treatment” (AIH 2007).
Homeopathic medicines, which are made from plants, minerals, metals, synthetic
chemicals and other substances, are developed to address a specific symptom, or set of
symptoms, which have been revealed during an extensive interview and examination of
the patient. Symptoms are ranked (common, general, concurrent, and local) and a
remedy is selected, typically “one medicine at a time” though “complex homeopathic
medicines . . . several medicines mixed together” may be used (Skinner 2001:19).
Homeopathy is based on “principles” that guide the diagnosis and treatment of
imbalances in the body, which if left unchecked, eventually lead to sickness and disease.
The principles, as stated by the American Homeopathic Association include:
1. Maintenance of normal health depends on efficient physiological functions as
controlled by a complex regulating mechanism designated by the term
homeostasis.
2. When threatened by disorder or disease, all living organisms exert an effort to
maintain or regain normal physiological equilibrium.
3. Recovery from disease is dependent on the inherent vital force of the
organism, i.e., its ability to re-establish homeostasis.
4. In general, most human disorders possess two components, the psyche and the
soma, which produce emotional, mental, and/or physical symptoms.
5. The human organism, by virtue of such inherent properties as sensitivity,
irritability, and reactivity, may be provoked into some physiological responses
by various types of physical, chemical, or biological incitants. When caused
by a drug, this is regarded as an iatrogenic response or reaction.
6. A substance which is capable of evoking certain symptoms when administered
to an apparently healthy human being under controlled conditions, may
become a potentially effective therapeutic agent when prepared according to
the standards of the Homeopathic Pharmacopoeia, and administered in
accordance with the principles of the Homeomethodology. (AHC 2007:n.p.)

Considered an alternative or complementary form of medicine or therapy in the
United States, homeopathy is one of four systems of medicine available to both adivasi
and non-adivasi populations in India today. The practice of homeopathy “sneaked into
India stealthily and traveled to Calcutta through Lahore, the first place of its exposure,
patronage, grooming and interaction” (A. Kumar 1998:62), having been “practiced . . . by
some of the Europeans before the mid-nineteenth century (Nagla 1997:49).
Practitioners of homeopathy, or homeopaths “define health as a state of freedom
existing on three interrelated levels: the physical, the emotional, and the mental”
(Cummings and Ullman 1984:17). When a patient sees a homeopath for treatment he or
she will undergo a thorough examination and interview with the clinician to determine
what is going on with the patient. This is a somewhat lengthy process as the homeopathic
practitioner needs to know about what is going on with the entire person. Skinner notes
that,
The pattern of physical symptoms as well as alterations in cognitive and
emotional functioning of a patient are evaluated holistically by a clinician. The
complete symptom set is then matched with the complete symptom set of a
group of healthy subjects who have all taken a medicine as participants in an
experimental trial. The medicine that is most parallel to the person’s state of
illness is then prescribed as an ultradilute aqueous solution, or as sugar pellets
medicated with a solution. (Skinner 2001:4)
The interview is very critical to the accurate appraisal and diagnosis of the patient’s
condition, as homeopathy treats the entire person, rather than just addressing a symptom
or cluster of symptoms (Skinner 2001). Regarding the practice and efficacy of
homeopathy, Reilly writes that “medical care must now consider the implication that
enhanced human healing, with less side effects, can be achieved with better time and

therapeutic consultations” (Reilly 1998:118), something frequently absent in biomedical
systems of health care and healing.
Whiteford has studied the use of homeopathy in a community in Oaxaca, Mexico.
Whiteford (1999) interviewed 174 male and female patients, looking for gender
differences as to the efficacy of homeopathy as a treatment. Whiteford found that
“homeopathic physicians and care fit nicely into this panorama of curing alternatives.
Many people feel that illnesses that are not responsive to Western medicine are often
effectively treated by homeopaths” (Whiteford 1999:70), having been practiced in
Mexico for about 150 years. He also found that women reported more frequently than
men that homeopathy was effective in treating the malady for which they sought
treatment.
Unani Tibb: An Ethnomedical Blend
Unani Tibb, which has also been referred to in the literature as Yunani medicine
(D. Kumar 1997:180), is an indigenous practice of health care and healing practiced
today in India as well as other parts of South Asia. Unani “means Greek [Ionnian] and
Tibb, from the Arabic, means medicine” (Sheehan and Hussain 2002:123). Unani “has
been part of the Indian medical repertory for many centuries” (Liebeskind 2002:59),
though no one individual has been credited with its establishment. Unani is based on
Greek medicine, though Arabic medicine is considered its “progenitor” (Sheehan and
Hussain 2002:123). Unani has been influenced by practitioners in West Asia and the
Middle East, specifically Ibn Sina, a Persian practitioner.

Unani is based on a humoral medical system, which emphasizes the bodily
humors. Health occurs when the humors are in balance. Imbalance results in a variety of
diseases. Each individual’s personality is said to be determined by one of the bodily
humors. Unani medicine is practiced by a hakim (physician) and is found predominately
among Muslim or Islamic populations within South Asia. The philosophical focus of
unani is that humanity and nature coexist, with humanity adapting to accommodate
changes in nature such as climate, temperature, etc. (Sheehan and Hussain 2002:125).
Balance among the bodily humors is critical to good health. The hakim, when examining
a patient, will look for imbalances within the patient, conducting an examination which
includes discussing with the patient his or her activities of daily living, problems with
appetite, sleep, and specific complaints. Once a diagnosis has been made, treatment will
focus on restoring the body to balance. This could include massage, cupping, Turkish
bath, diet or drug therapy, as well as many other options, depending on the needs of the
patient (Sheehan and Hussain 2002:126).
Liebeskind notes that “there has never been a disciplined and homogeneous
community of practitioners on Unani medicine” (Liebeskind 2002:60), with the training
and practice of each practitioner varying from somewhat scientific (as it relates to drug
therapy) to philosophical. Unani tibb has seen its share of disputes with the biomedical
community as to its place among science-based methods of health care and healing.
Education in unani tibb today consists of training similar to that for biomedical
practitioners, with students obtaining a bachelor of Unani Medical Science (B.U.M.S.).

Students may then register with the state government and practice unani medicine
(Sheehan and Hussain 2002:130).
The Biomedical System of Health Care
Allopathy, which is also referred to as biomedicine, conventional medicine,
Western medicine (Hahn 1995; Kleinman 1980, 1988; Konadu 2007), “cosmopolitan
medicine” (Loustaunau and Sobo 1997; Rubel and Hass 1996), “clinical medicine”
(Loustaunau and Sobo 1997), or “scientific medicine” (Finkler 1998:118) is one of the
primary health care services available to adivasi and non-adivasi groups in India today.
The “bio” in biomedicine “suggests that health and wellness are physiological issues,
which are the focus of the medical model” (Loustaunau and Sobo 1997:3). Allopathic or
biomedicine (the terms may be used interchangeably), is “generally believed to operate in
a realm of ‘facts’ . . . where illness is thought of as a ‘natural’ occurrence” (Rhodes 1996:
166)—everyone gets sick at some point in their lives. Allopathic medicine is:
What most of us understand to be “standard” or “regular” medicine . . . legitimate,
true and credible . . . it is that practice which combats disease by use of remedies
producing effects different from those produced by the disease treated, including
the use of all measures that have proved to be of some value in the treatment of
disease. (Nagla 1997:46)
Allopathy “focuses on disease control and approaches body parts as discrete and
mechanical” (Dei et al. 2000:172). Disease “can be defined as an ‘impairment of health
and well-being.’ Indeed, good health would be freedom from disease” (Mascie-Taylor
1993:1). Allopathic medicine is found around the world and may be considered the gold
standard by many due to its scientifically-based principles and laboratory tested treatment
modalities. A significant point about biomedicine is that, “Because of the disease

orientation of biomedicine and the tendency to medicalize or reduce problems to the
organic level, recommendations for diagnosis and treatment did not, until recently, begin
to include consideration of cultural beliefs, values, or practices” (Loustaunau and Sobo
1997:145).
Biomedicine “evolved out of a tradition of service to suffering humanity” based
on the Hippocratic Oath to do no harm (Loustaunau and Sobo 1997:126). The evolution
of biomedicine in India is disputed. Worsley states that Western medicine “had spread
via the Arabs, to India, by around 750 AD” (Worsley 1982:317), while Nagla credits the
British with the introduction of allopathic medicine to India (Nagla 1997:121). Kumar
notes that medical science “was introduced from the top by the colonial government on
and above the traditional medical sciences” whereby they “trimmed, shaped and
conducted the growth of Western medical science to attend, promptly and appropriately,
to the callings of the Empire” (A. Kumar 1998:17). The establishment of the Indian
Medical Service (IMS) was an effort to regulate the provision of medical services and to
keep Indian nationals who practiced biomedicine in a subordinated position to the
Anglos.
Whiteford observes that “For a variety of historical and cultural reasons, the
tensions between allopathic (or biomedical) and alternative medical models found in the
United States have not been so widely adhered to in much of the rest of the world”
(Whiteford 1999:69). Thus in non-Western cultures, there is greater acceptance of what
the West refers to as “alternative” or “complimentary” medicine, in part because they

have developed their own systems of healing that have endured for centuries, and may be
more readily accepting of newer, more scientifically-based methods, as long as these do
not conflict with traditional practices. Today, allopathic medicine is one of the primary
health care options available, to varying degrees, to adivasi and non-adivasi populations
alike.
Summary
The continuum of ethnomedical and biomedical health care-related services
available in India, including in Kawant and Kadipani villages where the Rathwa live,
work, and seek health care-related services creates a situation where consumers, or
patients, may be swayed by various factors when making health care-related decisions.
India has a long history of providing different ethnomedical health care and healing
options, such as the use of traditional healers, medicinal plants, and ancient practices such
as Ayurveda and Unani Tibb. Biomedical health care services are also available, creating
a dichotomy between traditional and modern, indigenous and scientific. Health care
decision making may be influenced by a number of variables such as, individual
experience with a particular health care provider, service availability, beliefs about health
and sickness, and personal issues such as gender, finances, and transportation.
CHAPTER FIVE
METHODOLOGY
Introduction
This chapter discusses the data collection methods I used for my research, why
each method was selected, how my entry into the field was facilitated, sampling

techniques for the two populations I was working with (Rathwa and HCPs), and my
experiences as a foreign woman in the field, as well as a participant observer, interviewer,
and surveyor.
Entry into the Field
My entry to the field was facilitated by Dr. Vijay Shah, my sponsor in India, who
is a medical doctor living in Baroda, a city about two hours drive from Kadipani and
Kawant villages. Dr. Shah is the medical director of the Indu Blood Bank in Baroda and
is involved in a variety of health-related projects in the area. Dr. Shah is a colleague of
Dr. Laurence Branch, a professor with the University of South Florida (USF) College of
Public Health (COPH). Dr. Branch approached Dr. Elizabeth Bird, Chair of the USF
Anthropology department and proposed a project examining health care practices in
India. Dr. Bird suggested that I consider conducting my dissertation research with an
adivasi group in Gujarat State, India under the mentorship of Dr. Shah.
Once in the field, Dr. Shah introduced me to Ramsingh Rathwa, a Rathwa adivasi
and former member of Indian Parliament. Ramsingh Rathwa had been the elected
political representative of the Rathwa adivasi of Kadipani in the past. Dr. Shah also
introduced me to Ramesh Rathwa, the Sarpunch, or elected local leader for Kadipani
village. Each of these men facilitated my entry into the field and my research in Kadipani
and Kawant villages in a number of ways, not the least of which included finding a place
to live, accompanying me to meetings with local officials, obtaining permission from the
Kawant taluka district officer to conduct my research in Kadipani and Kawant, getting
copies of local maps and property records for Kadipani, answering my many questions, as

well as introducing me to lots of people who could provide me with information pertinent
to my research.
Language Issues
When I entered the field, I was not fluent in Gujarati, the language spoken by
people living in both Kadipani and Kawant. I had received tutoring in Gujarati before I
entered the field, and I had a computer-based tool for learning the basics that I practiced
with regularly. I also purchased a number of Gujarati phrase books and dictionaries, and
working with my tutor, scripted out my introduction, which included my name, where I
was from, what my research was, why I was doing the research, and what I was hoping to
accomplish. After repeating this script many times during the survey portion of my data
collection, I became more comfortable with conversing in Gujarati. For the most part, I
relied on translators to help when I communicated with people who spoke only Gujarati.
Occasionally, I would meet someone who spoke English—such as some of the HCPs, the
local primary school teacher, employees at GMDC, or young people who received English
language training as part of their schooling.
Eventually, I got to the point where I could understand much of what was being
said to me, especially when asking questions for which there was a limited range of
responses. However, I still had difficulty correctly constructing a sentence in Gujarati in
response to their questions to me. I did on occasion make mistakes while speaking
Gujarati, saying “bes” (water buffalo) instead of “bas” (stop). This was a minor error
compared to one incident in which I was interviewing a woman about how she came to
be diagnosed with sickle cell disease. My translator and I were sitting with her outside,

all of us seated on boulders. By that point, I had surveyed or interviewed a number of
people and had developed some ability to follow the flow of conversation. The woman
was telling me how she had to have a caesarean section delivery for her first pregnancy.
It was during that period of hospitalization that she was diagnosed with sickle cell
disease. She was lamenting how she had much pain after the procedure and how she had
not felt the same since then—she believed that her health had deteriorated. I understood
some of her Gujarati, but I relied on my translator to translate in detail.
At one point I thought the woman said the Gujarati word for goat “bakaree.” I
said “bakaree?” questioningly, now feeling lost in the conversation. The woman tilted
her head to one side, said “bakaree?” and laughed so hard she practically fell off the
boulder. I realized I had misunderstood. We laughed over my mistake and proceeded
with the interview. Days later, while in the village center, I saw the woman’s husband
and his brother, both of whom I had met while conducting surveys. Her husband
approached and greeted me, laughing as he told me that his wife had mentioned the
“bakaree” story. So my lack of language fluency was sometimes both a technical barrier
and an aid to rapport.
Data Collection Methods
Anthropologists “collect data concerning the issues as participants see them”
(Loustaunau and Sobo 1997:160), a factor that is critical to collecting meaningful data.
When considering the health care and healing practices of the Rathwa, I kept in mind that
their concepts of health and sickness, as well as how they treat various illnesses was “a
function of the interaction between socio-cultural and socio-biological practices, the

genetic attributes, and environmental condition” (Paul 2005:258), all of which can and do
impact health care outcomes to varying degrees.
A variety of methods were used during data collection, both in Kadipani and
Kawant. Data collected were analyzed using Statistical Package for the Social Sciences
(SPSS) versions 16 and 17. My choice of methods was driven by my goal of building
rapport with participants, developing a relationship, experiencing their culture, and
obtaining data that was as accurate and as meaningful as possible. I believed that a
triangulation of methods would be the best way to ensure validity, as I was unsure how
factors such as being a foreigner, using translators, and personal bias (recognized or not)
might affect not only just data collection, but also subsequent analysis and interpretation.
My data collection methods included: participant observation in a wide variety of
settings (e.g., public clinic and hospital, private clinics, villagers’ homes, local market
[haat], temples, the village center, local shops, primary school, and on the roads within
and around the village); informal interviews with Rathwa living in Kadipani as well as
HCPs in Kadipani and Kawant; structured interviews with ethnomedical and biomedical
HCPs in Kadipani and Kawant villages (n = 19); structured interviews with a sample of
Rathwa living in Kadipani (n = 30); and household surveys of Rathwa living in Kadipani
village (n = 121).
I began my research by informally asking people “What did you do the last time
you were sick?” “What did you do the last time your child was sick?” “What makes
people get sick?” These questions led to a variety of responses, some more detailed than
others. At times I felt that participants were telling me what they thought I wanted to

hear, especially when I spoke with people about issues of concern to the Indian
government, such as where babies are delivered. Some participants quickly replied “I go
to the hospital” when asked what they do in response to just about any health-related
question.
What I discovered over time was that the response “I go to the hospital” was a
catch-all phrase for seeing any HCP within the government clinic and hospital compound
in Kawant, as well as the GMDC-sponsored dispensary in the center of Kadipani. The
government health care service complex in Kawant was a free service that anyone could
access, and the health care providers (nurses, one allopathic physician) moved between
the buildings seeing or monitoring patients, providing care, and dispensing medications.
Sampling for Informal Interviews
Non-probability sampling was used when I conducted informal interviews with
Rathwa living in Kadipani village, as well as those seeking services in the private and
public clinics and hospitals in Kadipani and Kawant, or any place where I had access to
Rathwa from Kadipani who were willing to talk with me. Convenience sampling was
utilized frequently while observing the provision of health care services. I was in the
right place at the right time to talk with people about health care and healing. Most
people were willing to talk and would tell me about many aspects of their lives.
I was cognizant that some individuals in poor health might not have the means to
seek medical treatment (money, transportation, assistance from others, strength/overall
health/ability to physically leave the home). I wanted to be sure that I spoke to those
individuals in their homes, as they might not seek services from an HCP for a variety of

reasons. Choosing not to receive health care, for whatever reason, fits into the equation
of my health care decision-making research question.
Sampling and Research Methods
Kish (1965, 1987), Sudman (1976), and Alreck and Settle (1995) write of the
importance of correctly designing a sampling method, or methods, to be used in a
research study. Sudman observes that “whether or not a sample design is appropriate
depends on how it is to be used and the resources available” (Sudman 1976:9). He also
notes that “data collection should be considered prior to making sampling decisions”
(Sudman 1976:15). The data collection methods I selected required me, as the researcher,
to be totally engaged in the research process and familiar with the population that was
sampled for each data collection method. The combination of research methods enabled
me to get to know the Rathwa and the HCPs in a way that may not have been possible if I
had chosen other or fewer methods. I was able to learn about each respective groups’
“culture,” as well as observe what they actually do when either providing or receiving
health care services, rather than just having them tell me.
Sample Size
Studman states, “a small study well-designed and executed is superior to a large
study that has been botched” (Sudman 1976:9). My sample size for each population
group (Rathwa adivasi and ethnomedical and biomedical HCPs) was relatively small. The
total number of households in Kadipani was 147, of which I surveyed 121. The total
population of ethnomedical and biomedical HCPs was approximately 25. I conducted
structured interviews with nineteen HCPs. I selected a random sample of Rathwa for

structured interviews (n = 30). My household surveys and structured interviews with
both population groups are discussed briefly below and in greater detail in Chapter
Seven.
Sample Populations
Samples were drawn from two population groups: (1) Adult male and female
Rathwa living in Kadipani; and (2) Ethnomedical and biomedical HCPs practicing in
Kadipani or Kawant. Samples were taken for three data collection methods:
1. Structured interviews with Rathwa living in Kadipani;
2. Structured interviews with ethnomedical and biomedical HCPs practicing in
Kadipani and/or Kawant.
Sampling Techniques
I used both probability sampling (utilizing a form of random selection) and
nonprobability sampling (e.g., accidental, haphazard, or convenience sampling).
Probability sampling is defined as a sample “in which every element in the population
has a known, nonzero probability of selection” (Kish 1965:20; Sudman 1976:49). A
variety of sampling techniques were used during data collection, each being dictated by
the data collection method I was using at a given time. During my pilot study in June
2007, I began searching for key informants via word-of-mouth recommendations, which
led to snowball sampling of additional participants. When I returned in November 2007,
I used word of mouth, as well as snowball sampling, to locate additional participants for
my population of HCPs (Handwerker and Borgatti 1998).

Section I—Key Informants/Participants
Rathwa Adivasi of Kadipani Village
To be included in any of the data collection, participants had to: (1) self identify as
Rathwa; (2) live in Kadipani; (3) be an adult Rathwa male or female (a person 16 years or
older); and (4) agree to be interviewed. An informed consent form approved by the USF
IRB was read in Gujarati to each potential participant as the Rathwa neither read nor
write any language. The USF IRB waived the requirement for written informed consent
for this research. Once the individual understood what was involved and agreed to
participate, they were interviewed.
The sampling technique I used for informal interviews with Kadipani villagers in
both Kadipani and Kawant was opportunistic and haphazard—I spoke with whomever
was willing to talk with me. This was a very efficacious method in that I got to know
people in the village, found out who was related to whom, where people lived within the
village, what they did for work, the crops they grew, how many children they had, and
quite importantly, what they did when they or a family member got sick. I also used
snowball sampling with the intent that a conversation with one key person could lead to a
conversation with another key person, such as one of their friends, family members, or
colleagues, especially other HCPs, who had information I needed. For the structured
interviews with Rathwa, a random sample (n = 30) was taken from the total Kadipani
Rathwa household population, information provided to me by local serpunch in the form
of property records.

I was concerned about the potential for bias from “errors of non observation”
(Kish 1965:527). Prior to beginning my fieldwork, I did not know if foreign researchers
had worked in Kadipani or Kawant in the past. There was the potential for non-response
due to refusal to participate. I did not know how receptive the Rathwa would be to:
(1) allowing me into their homes; and (2) speaking with me about their health care and
healing beliefs and practices. In addition, non-response due to people not being at home
when I came to their residence was a concern. Visiting the home during the day, I could
miss people who were temporarily unavailable, such as when they are away at work, at a
medical clinic, shopping, caring for a neighbor or family member, etc. When this
occurred, I called back on households (Kish 1965:350). I worked only during daylight
hours, as I was advised by multiple people not to be in the village after dark.
Ethnomedical and Biomedical Health Care Providers in Kadipani and Kawant
To be included in the structured interview portion of my data collection,
individuals had to: (1) be either ethnomedical or biomedical HCPs (e.g., bhouas,
Ayurvedic, homeopathic and allopathic doctors; (2) work in Kadipani or Kawant; (3) treat
or have treated in the past Rathwa living in Kadipani for any illness at any time; and
(4) agree to be interviewed. An informed consent form approved by the USF IRB was
read in Gujarati to each potential participant, as Gujarati was the primary language for all
participants. Once the potential participant understood what was involved and agreed to
participate they were interviewed.

Section II—Structured Interviews
Structured interviewing requires the use of an interview schedule or questionnaire
comprised of questions that structure participant responses (de Munck and Sobo 1998:
260). My purpose for conducting structured interviews with HCPs and the Rathwa was
to collect: (1) in-depth information on topics related to health care and healing practices;
(2) personal histories, specifically examples of what healing or health care practices have
or have not worked in the past; (3) cultural knowledge and beliefs about healing and
health care, especially as they relate to indigenous knowledge; as well as (4) a
description of health care and healing practices (Lecompte and Schensul 1999a). My
HCP and Rathwa structured interview forms had open and closed response questions and
were designed to elicit information that would facilitate my understanding of how these
two populations conceptualize sickness and health.
Rathwa Adivasi of Kadipani
Structured interviews were conducted with Rathwa living in Kadipani (n = 30).
My sampling frame, or list of potential participants, was provided to me by different
sources. For the structured interviews with the Rathwa, I used area frames for
households (Kish 1965:301). I had a list of who owned what piece of property in
Kadipani village, as well as a map of households within Kadipani. I randomly sampled
Rathwa households
for my structured interviews from the property list. There were 147 properties on the list.
I wanted to interview 30. Assuming a 60 percent cooperation rate, I selected 50. One
hundred forty-seven divided by 50 is 3, making my sampling interval 3. I selected a

random number between 1 and 3, and that was my random start on the ordered list of
properties.
The structured interview instrument contained 26 open and closed response
questions designed to elicit information about health care and healing practices as well as
health care-related decision making. Interviews took place at the participant’s residence
and lasted approximately 30 minutes, depending on how lengthy the participants’
responses were and the health status of the people in the household (in a household with
more sickness, the respondent had more to say).
Questions were both closed and open-ended, with time at the end allotted for the
participant to share with me anything that was not included in the interview instrument.
Most people were very talkative when discussing the health of their families, especially
when asked what health care services they do not currently have but would like. The
Rathwa structured interview instrument is attached as Appendix A.
Ethnomedical and Biomedical HCPs Working in Kadipani and Kawant
Structured interviews were conducted with ethnomedical and biomedical HCPs
(n = 20 out of 21; a 95 percent response rate) in both Kadipani (e.g., bhouas, Ayurvedic,
homeopathic and allopathic) and Kawant villages (Ayurvedic, homeopathic and
allopathic). I was told there were approximately 20 Ayurvedic, homeopathic, and
allopathic HCPs practicing in Kadipani and Kawant. My intent was to interview all of
them. I interviewed 16. Reasons for not interviewing the remaining four HCPs include:
(1) refusal to participate; or (2) no one present at the clinic location despite numerous
visits. I also interviewed one traditional birth attendant who lived in Kadipani.

I used judgmental sampling intentionally seeking out particular individuals who
were specialists in the health care practices in which I was interested(Agar 1996:168). I
asked the allopathic doctor to tell me if there were any other allopaths practicing in either
Kadipani or Kawant, and how I could get in touch with them. I also asked the Ayurvedic
and homeopathic doctors to tell me of other Ayurvedic and homeopathic doctors
practicing in Kadipani and Kawant and how I could get in touch with them. All
allopathic, Ayurvedic, and homeopathic HCPs had an equal opportunity to be included.
This was a fruitful sampling technique, as invariably I was directed to other HCPs,
including their names and where to find them.
Bhouas were not included in the HCP interviews for Kawant as the Rathwa visit
bhouas living in Kadipani, their home village. I asked all HCPs, the Kadipani village
leader, and other people to tell me who in Kadipani was a bhoua, and how I could get in
touch with these men. This technique resulted in bhouas being brought to me. Bhouas,
unlike the allopathic, Ayurvedic, and homeopathic doctors, do not have clinics or spaces
dedicated to treating those in need. The bhouas are Rathwa who live in Kadipani, and are
farmers just like so many other Rathwa, in addition to practicing as a bhoua. Bhouas
typically go to the home of the person who is sick, especially if that person is seriously
ill, debilitated, or unable to travel to the bhoua’s home. I also asked all HCPs and local
government officials to inform me of any Unani Tibb practitioners in either Kadipani or
Kawant. There were none, most likely due to the absence of Muslims living in these
villages.

Structured interviews with HCPs took place in the individual’s place of practice,
except for the bhouas, who were brought to me, and lasted between 30 to 60 minutes
depending on how talkative the individual was, if they had a large clinic and they wanted
to show me around, how busy they were with patients, as well as their general interest in
my research. My HCP structured interview instrument includes both open and closed
response questions and is attached as Appendix B.
Section III—Household Surveys
The term survey “refers to systematic data collection about a sample drawn from a
specified larger population” (Schwarz et al. 1998:143). Surveys enable a researcher to
collect a significant amount of data “in which a large number of people, generally a
carefully selected sample, are polled” (Loustaunau and Sobo 1997:160). My goal with
conducting household surveys was to collect culturally relevant data related to how the
Rathwa conceive of health and illness, the range of health care services available to them,
their use of home remedies and locally grown medicinal plants, what HCPs they typically
seek services from and why.
My purpose was to determine “variations in attitudes, knowledge, perceptions,
demographic information and behavior” (LeCompte and Schensul 1999a:128), to reach a
relatively large percentage of the total population, and to obtain data that may be made
quantifiable. Surveys were critical to my work, as I was examining not just what people
believe or think about health and sickness as well as health care practices, but what they
do with these beliefs and practices—how they translate them into behavior, specifically
health care practices and decision making.

My questionnaires s consisted of two types of items: close-ended or forced
response questions which prompt participants to select a response from a number of
options (approximately 3- 5 response options, depending on the question), and openended
questions which invited participants to respond as they chose. I developed the survey
instrument after spending time talking with people about their health care practices,
conducting some informal interviews with both Rathwa and HCPs, and consulting with
my sponsor, Dr. Vijay Shah. Survey questions were of nominal (e.g., gender), ordinal
(e.g., Likert scale response options such as strongly agree, agree, neither agree or
disagree, disagree, strongly disagree) and interval (age, income, etc.) scales. My goal
was to get quantifiable data from this research method, or get data that could easily be
quantifiable. I wanted not just descriptive statistics from this project, but also inferential
statistics—what could I infer or predict about the population from their responses?
Prior to entering the field I was briefed by my sponsor, Dr. Vijay Shah, on village
household protocol—who I should speak with first when approaching a house and asking
if someone would be willing to speak with me. I was told that there would be an adult
male home at all times with the women and children, but this was not always the case.
Frequently. I found myself in households where only females or only males were home.
Household structure, people who were at home, and those who had the time and
inclination to speak with me are indicated in respondent distribution by gender. More
females were available and willing or interested in participating than males.
Household socioeconomic status (SES) varied, with indicators of SES including:

house size (number of rooms) and composition (brick, wood, sticks, tree branches, thatch,
cow dung); household monthly income; access to electricity; and material goods. Survey
respondents were asked to indicate if their household had any of the following items:
chair, table, cot/bed, mattress, bike, scooter, car, radio, television, mobile phone, number
of livestock, animals-drawn carts, electric fans, etc.
My goal was to survey all Rathwa households in the village. Reasons for less than
100 percent coverage included: (1) no one was home despite multiple visits; (2) no adult
was home, only young children; (3) residents declined to participate; (4) residents were
not Rathwa (being, for example Bhil, Nayaka, or non-adivasi, who were not included in
the survey). Survey data were collected from 121 of 147 households in Kadipani village.
The English version of the Rathwa household survey instrument is attached as
Appendix C. The Gujarati version of this same instrument is attached as Appendix D.
Issues of Understanding
Before, as well as during, the time I was conducting structured interviews and
household surveys, I was cognizant of how difficult a process this could be for a number
of reasons, not the least of which are cultural-bound meanings and concepts. I tried to
structure my questions carefully and in a culturally appropriate manner (Schensul et al.
1999:4), recognizing that words may have subtle differences in meaning depending on
who is saying them and within what context. Much information may be “lost in
translation” not only when trying to develop something like a cross-cultural survey (Baer
and Weller 2006), but also when trying to communicate with a group that has its own
particular slang, vernacular, or dialect.

I was told by my sponsor that the dialect of Gujarati changes every twelve
villages. My translators were from Baroda, which is approximately a two-hour drive
from Kadipani and Kawant. I was thus concerned about how changes in dialect might
lead to misunderstandings. For some questions, especially those related to sickle cell
disease (SDC), sickle cell anemia (SCA), and sickle cell crisis (SCC), I suspect some
people did not really understand what illnesses I was talking about.
After I completed my data analysis and reviewed the results, I began to consider
if people had responded in a way that they thought I would like them to respond. I also
considered if the symptoms of the diseases that biomedicine refer to as SCD, SCA, or
SCC may be perceived by the Rathwa as just part of living an extremely hard and
physically demanding life. They have joint pain and fatigue from the work their lifestyle
demands. It may be that some do not differentiate these symptoms caused by hard living
from those of SCC. This concern certainly opens the door to further research on the
incidence of sickle cell disease, as well as peoples’ understanding of what the disease is
and how it may manifest in one’s life.
Rathwa Adivasi Households in Kadipani
Household surveys were conducted of Rathwa living in Kadipani village. Once
had an idea of how the Rathwa conceive of health and illness, I drafted an instrument for
surveying households within Kadipani. During my surveying, I discovered that most of
these households were occupied by Rathwa, though some were other adivasi, either Bhil
or Nayaka, or non-adivasi, including people who had moved to the area to work for

GMDC. Non-Rathwa household were not included in the survey as the goal was to study
health care and healing practices among Rathwa only.
There were 147 households in Kadipani. I surveyed 121 of those households, an
82 percent response rate. Twenty-six households were not included in the survey for the
following reasons: (1) residents did not self identify as Rathwa (they were Bhil, Nayaka,
or of some other adivasi or non-adivasi group [n = 10]); (2) no one was present at the
residence despite repeated visits to the home (n = 9); (3) individual(s) in the home refused
to participate for a variety of reasons (too busy, husband not present to give permission,
not interested [n =7]).
Research Assistants
I hired 11 local health care workers from the Kawant taluka office to assist me
with surveying households in Kadipani (Figure 6). I conducted surveys with the
assistance of my translators at the same time that the survey workers were conducting
surveys. We were all in a single location of the village simultaneously, moving as a
group from one location to the next, broken up into pairs, to survey all of the Rathwa
households in that location, then moving on once we had covered a specific location
within the village. Houses tended to be in clusters, typically around a water source such
as a hand pump or tap, so it was relatively easy to complete a grouping of houses before
moving on to the next grouping.

Figure 6. Research Assistants on first day of survey data collection.
Ten of the research assistants were women; one was a man. Nine of the research
assistants were Rathwa themselves, one of whom, the man, lived in Kadipani. The fact
that the research assistants were Rathwa was a great advantage. I believe my project was
more easily accepted by Kadipani Rathwa because they were being surveyed by people
with whom they shared a common identity. Villagers also knew many of the research
assistants, as they had conducted health-related work in Kadipani in the past. They also
assisted with heath-related education programs at the government sponsored clinic and
hospital in Kawant, such as the family planning female sterilization camp.

Research Assistant Training, Compensation, and Recognition
Prior to the beginning of survey data collection, I held a training session (Figure
7) during which I: (1) introduced myself, as well as Dr. Vijay Shah, my sponsor, and
Ankita and Hatel Patel, my two translators; (2) provided each research assistant with a
copy of the survey instrument; (3) reviewed the questionnaire, explaining each question
with the translation help of Dr. Vijay Shah; (4) explained the intent of my research, the
focus of each question, and what I hoped to achieve; (5) explained each research
assistants’ responsibilities; and (6) discussed the approximate timeline for completion of
the survey portion of my research.
Figure 7. Research Assistants on training day.

At the end of the survey data collection portion of my research, I paid each
research assistants 50 rupees per day worked, an amount negotiated by Dr. Vijay Shah
and myself with Somoiben B. Chaudhari, Child Development Program Officer for
Kawant taluka district office who is also the research assistants’ supervisor. Upon
completion of the survey portion of my data collection, I held a recognition ceremony
(Figure 8) for the research assistants, during which Somoiben B. Chaudhari, Child
Development Program Officer for Kawant taluka district office and Mr. P. K. Mackwana,
Kawant taluka development officer, were present. Each research assistant received his or
her pay in a pretty envelope, was given a small memento of appreciation from me, as well
as a certificate of recognition signed by me with the University of South Florida logo on
it. In addition to the recognition ceremony, that same day we made a field trip by jeep to
a beautiful temple in Hafeshwar, during which we stopped at the Narmada River for a
ritual bath, collected Narmada River water in plastic bottles I had from my time at the
guesthouse, and participated in prayer and worship. I discuss this event and its
significance in greater detail later.
Survey data collection took 6 days. Research assistants worked in pairs, a practice
they follow when doing their public health-related work in the local villages. I was
advised to do the same for my work. Each morning we met at the GMDC guest house.
One research assistant, Daxshaben Trivedi, was the research assistants’ direct supervisor
at the taluka office. She was also responsible for supervising the research assistants

during my project. I had the research assistants sign in each day so I would be able to
accurately calculate their wages once survey data collection was completed. Every day I
Figure 8. Research Assistant recognition ceremony.
distributed a stack of blank surveys to each research assistant along with a pen for his or
her use and a piece of chalk for marking the entrance to each house so we knew if: (1) a
survey was completed; (2) the household refused to participate; (3) no one was home; or
(4) the residents were not Rathwa.
Research assistants were also provided with small items such as pencils and
trinkets to be given as tokens of appreciation to the survey participant at each household.
Each day, we rode by jeep as a group to a pre-designated starting point in Kadipani and
then determined which pair of workers would go to which house. We split up, surveys

and tokens of appreciation in hand, and proceeded with our work. Research assistants
were instructed to survey only those households in which the people were Rathwa, to
read the consent at the top of each survey, and to proceed only if the person understood
and agreed to participate. Completed surveys were collected by me at the end of each
day, as was information about: (1) how many households refused to participate; (2) how
many households where no one was home; (3) how many households were not Rathwa. I
then compiled these data for each day, and reviewed each survey for thoroughness,
problems, confusion, etc. The Kadipani Village Household Survey form, English
version, is attached as Appendix C, and the Kadipani Village Household Survey form,
and the Gujarati version is attached as Appendix D.
Section IV—Participant Observation
Participant observation was the data collection method used most frequently.
While living in Kadipani I was able to move about the village, visit with people, meet
their family members, see their children, livestock, and farm plots, talk with local HCPs,
and see for myself how people conducted their daily lives, especially as it related to their
health care needs and health care decision making. It is impossible to describe all that I
saw—a newborn baby just minutes old, homes with intricate designs on the floors,
beautiful artwork, massive piles of corn being processed, lots and lots of children, an
elderly man in cardiac arrest surrounded by his family members, many altars dedicated to
a variety of Hindu deities, and so much more.
There were two primary schools in the Kadipani area, one where Rathwa children
primarily attended, another closer to GMDC where children of GMDC employees

attended. I visited both primary schools, met the school teachers, and donated school
supplies (paper, pencils, pencil sharpeners, markers, colored index cards, and other items)
to the schools. I had met one of the school teachers, a young man, during my preliminary
visit in June and he remembered me. Subsequently, I occasionally ran into him in the
village; he spoke very good English and was interested in my research.
Within the broader region where the Rathwa live (meaning not just Kadipani and
Kawant, but also beyond), I observed two main economic operations, first the GMDC
mining operation within Kadipani village, where fluorspar is mined and processed; and
second, cotton growing, ginning, and processing in Bodeli, a village that is over an hour
from Kawant and is much larger than Kadipani or Kawant. Gujarat Mineral
Development Company, “India’s premier mineral development company” (GMDC
2009:n.p.), has an active mining operation in Kadipani where the Rathwa reside. With
corporate offices in Ahmedabad, Gujarat State, GMDC has a state-wide and national
presence, as well as a local presence in Kadipani where fluorspar is mined and processed.
The mineral fluorspar is used “directly or indirectly to manufacture products such as
aluminum, gasoline, insulating foams, refrigerants, steel, and uranium fuel” (United
States Geological Survey 2009:n.p.).
I photographed and video-recorded many events, such as when I spent a Monday
afternoon at the haat (large local market), a man demonstrating for me how a bhoua heals
people, and people moving about the village, doing what they do. Participant observation
helped me feel a part of what was going on. It also provided me with entrée to people’s

homes. After seeing me repeatedly in the villages, eventually someone would approach
and ask when I was coming to their house.
Rathwa of Kadipani
I spent a considerable amount of time in peoples’ homes, as well as in various
locations in Kadipani. While walking through the village, people would occasionally call
out and motion for me to come to where they were. I did not have to be fluent in Gujarati
to know what people were saying to me, as I could typically tell from the quizzical looks
on their faces. Everyone wanted to know who I was, why I was there, what I was doing,
where I was living, and would I come see their home and sit with them. I was able to
introduce myself in Gujarati and tell a little bit about my research, but relied on my
translators for help with more complex conversations. At times conversations could
become very busy—lots of people talking at the same time, some taking me by the hand
to show me something, or young children coming close to look at me or ask me to take
their picture.
After a few days in the village, people who had seen me on a prior occasion would
approach, say hello, and then go about their work. I spent time with a woman observing
her make cow dung bricks which are used as fuel for cooking. When I asked if I could
try it, she looked at me and said no, that work was not for me. So I sat and watched,
talking about what she was doing, step by step. This woman was a widow with two
teenage daughters. Both daughters had contracted polio as babies, and their legs were
now wasted and folded beneath them. Neither was able to walk, instead moving about by
using their arms and swinging their lower half forward. Each girl worked outside

processing crops during my visits to the home. On my final day, they asked me to take
their photo and then wanted to see the image. They giggled and became shy when
looking at the digital photo, a response many people had when I showed them photos I
had taken. Needless to say, I was surprised at how many cases of polio I saw while in the
local villages and in other parts of India.
Rathwa Homes in Kadipani
Rathwa homes were clustered around water sources, such as a hand pump, well,
or tap. I learned the hard way not to attempt to collect data in this area of the village
during water availability time, as people were either not home or too busy with
waterrelated chores to speak with me. I called back numerous times throughout the day
to catch those people I had missed because they were out doing laundry or getting water.
Kadipani houses ranged in size from 1-4 rooms, with “wealthier” families living
in large, multi-room homes built from bricks and other materials with neighboring homes
some distance away. Poorer families lived in single room homes, or huts as they referred
to them, made of tree branches, sticks, cow dung, and thatch roofs. Neighboring homes
were close, with some practically on top of each other, their walls almost touching. This
close proximity of homes might be advantageous for a few reasons, not the least being
that during monsoon season the brunt of the driving wind and rain could be weathered
better by the structures collectively rather than singly. Severe rain could result in much
devastation, a result of how the homes are constructed, their locations, which were
frequently on hilltops or hill sides, and the fact they are surrounded by unplanted dirt that
could slide or erode with a strong downpour.

The Rathwa are patrilocal and patrilineal, tending to live in multi-generational
families. When a son marries, his bride moves with him to the house of his parents where
she helps her mother-in-law with household responsibilities and farming work. When the
number of people in a household becomes too large, someone—typically an elder son—
may build another home close to his family of origin where he, his wife, and their
children live. Ninety-five percent (n = 115) of survey respondents reported that they own
their own homes. The remaining respondents were renters or they lived in a home owned
by a family member.
Rathwa Livelihood
Rathwa farmers grow different crops, though most plant maize, which is
harvested, dried, processed, and used for making food. One “wealthy” farmer owned
land where he grew maize, wheat, pulses (lentils), and a variety of fruits and vegetables
(onions, potatoes, etc.), and he and his wife operated a small shop attached to their home.
In this shop they sold their surplus crops, along with some common household items and
tobacco products. This farmer had access not only to a nearby hand pump for water, but
he also had a well on his land for irrigating his fields and watering his livestock. He had
several large mature trees, including a huge mango tree, bamboo (used for housing
material and other things), small plots of land staked out where he and his wife grew
various herbs and other plants, as well as lots of goats, chickens, and a bullock.
I spent quite a bit of time with this farmer and his wife, who lived with their two
young sons in a brick home on top of a hill relatively far from other homes in Kadipani.
This home had four separate rooms with beautiful detailing in the cow-dung floor. The

detailing was created by his wife, who used the palm of her hand to make a half-circle
configuration to create the design. He was very proud to give me a tour of his home,
showing me where he had chickens roosting in small baskets that hung from the wall, a
large kitchen where shiny metal utensils, plates, and cookware were displayed neatly on
shelves, and a variety of colorful posters honoring Hindu deities. I spent a lot of time in
this household for a number of reasons, not the least of which was that this man was very
accommodating, liked to talk, and he wanted to introduce me to his neighbors. He was
very interested in my research and had number of comments to make about the
availability of health care services for the Rathwa. I videotaped our tour of his home,
which includes his explanation of the use of some of the articles hanging on the wall. He
also showed me two hens nesting in hanging baskets. He pulled out an egg one hen was
sitting on which caused her to loudly squawk! I was informed that the egg “was full”
(there was a baby chick inside). He replaced the egg and we continued on our tour.
This farmer, who was 22 years old when I met him, had been diagnosed with
sickle cell disease at a young age after he had fallen out of a tree due to giddiness (the
sense that you are moving/spinning while all else is still—not the same as dizziness).
Interestingly, he reported no cases of malaria within his immediate family (himself, his
wife, and their sons) or his extended family (his parents and siblings). This man also
provided me with a lengthy and amusing demonstration of how a bhoua conducts a
healing session, which I video recorded. When I played back the recording for him and
his neighbors, there was lots of laughing and excitement, with many people coming over

to view the playback, including the village leader’s mother who turned up frequently
while I was in various locations at the village.
In contrast to this respondent, whose home was located far from the center point
of Kadipani village, other people who lived near the center of the village, which is close
to GMDC, had less opulent living quarters. People who lived near GMDC had very
small homes, which they referred to as huts. These were typically one-roomed and were
constructed of tree branches, sticks, cow dung, and low, thatched roofs. These houses
appeared to be fragile structures that would need regular attention to keep the walls and
roof intact and animals and rain water out. These homes were small and crowded close to
neighboring homes, all of which were arranged in close proximity to the local water tap.
Water flowed from the tap only during certain times of the day, so activity around the tap,
such as washing clothes, or collecting water to carry home for cooking and drinking, was
at its peak early in the day when the water was running freely.
Gujarat Mineral Development Corporation (GMDC) in Kadipani Village
The presence of GMDC, a large commercial enterprise and employer in Kadipani
village, directly impacts not just local and individual household economies by providing
Rathwa GMDC workers with more disposable income than others, but it also influences,
both positively and negatively, individual and household health status. The health status
of those Rathwa who work for GMDC may be affected by on-the-job injuries,
stressrelated illnesses, or exposure-related diseases. However, they have greater ease of
access to heath care services than people not working for GMDC. These factors impact
health care seeking behavior, as well as health care decision making; more income allows

easier payment for health care services, and thus one’s choices are expanded. People who
have money do not have to seek services from the government sponsored clinic or
hospital unless they want to.
Malaria in Rathwa Households
During my time with the Rathwa, I spoke with people about malaria in order to
gauge their level of knowledge about the disease. Many households had had multiple
members who had suffered from malaria, while others had none. One young mother
reported stated that she had contracted malaria during her pregnancy and had been very
sick. She gave birth to a healthy baby and had one recurrence of malaria postpartum.
Rathwa knowledge about malaria varied, with some households taking preventative
measures such as sleeping with bed nets, covering water vessels where mosquitoes could
breed, and using various concoctions of neem to both prevent and treat malaria, and other
households doing nothing. Almost everyone was familiar with the anti-malarial
properties of neem, a tree that grows locally and to which people have easy access.
Health Care, Travel Distance, and Transportation
Rathwa frequently travel from Kadipani to Kawant for health care. The need for
some form of transportation (scooter, car, bus, jeep, truck, horse, walk) was a key issue.
While people could use the GMDC dispensary in Kadipani, it was staffed by a male
medical assistant, not an ethnomedical or biomedical doctor—a key factor in some
people’s health care decision making. There had been a government-sponsored clinic in
Moti Chikhli, which is not as far from Kadipani as Kawant, but this small facility closed
during my time in Kadipani and patients were told to go to Kawant for health care.

Seventy-five percent (n = 91) of survey respondents said that the distance they had to
travel to get health care was a problem, and 86 percent (n = 104) said transportation was a
problem.
While driving between Kadipani and Kawant, I frequently noticed TaTa pickup
trucks, busses, or jeeps packed with people, including those riding on the roof, who
would jump on or off at various points between the two villages. Once, while informally
interviewing a couple waiting for transportation to Kawant outside a small shop up the
road from GMDC, a small crowd began to gather. Their gathering had nothing to do with
their curiosity about me. They were all on their way out of town, each one piling into the
TaTa truck until it was overflowing, people hanging off the doors and windows, clinging
to the roof. Regardless where people were on the vehicle, they still had to pay for the
ride.
Rathwa Healing and Health Care Practices
Healing and health care are “concerned with the patient’s culture, his personality,
his norms and values (Nagla 1997:93). This is evident in the healing and health care
practices I have observed among the Rathwa in Kadipani. The Rathwa and the HCPs
who provide health care for them operate within a “‘metamedical’ framework of thought”
(Worsley 1982:315) particular to their culture, their history, and their traditions. It
became clear to me that the “ways in which we perceive and interpret health and illness,
and seek and deliver care, are inextricably bound up with cultural norms, beliefs, and
values, as well as with social structure and environmental conditions” (Loustaunau and
Sobo 1997:1).

I noticed on numerous occasions while observing in both public and private
clinics, that most, if not all, patients were accompanied by someone else, or multiple
people when they came to see the HCP. Those in dire need, who were too sick to walk,
were carried into the facility. Such was the case I discussed earlier for KaaKaa (uncle)
who, while in cardiac arrest, was wrapped in a blanket and carried from the village into
the public hospital in Kawant by his family members, where he was placed on a narrow
wooden bench outside the exam room until Dr. P. was able to see him. KaaKaa’s family
stayed with him the entire time he was in the hospital, and later that day they carried him
back home to die.
I also observed a similar case in a private clinic where a young woman
accompanied her elderly grandmother who had right-sided paralysis and needed the
added support of her granddaughter to make it into the clinic. In yet another clinic, I
observed a gaunt, middle-aged man come in surrounded by five other people. The man
had a head injury, wore a bloody makeshift dressing on his head and had blood stains on
his shirt. The doctor remarked to me that this man must be a very important person in his
village for so many people to accompany him to the clinic.
Rathwa Perceptions of Bhouas as Healers
What was interesting as well as perplexing during my observations in Kadipani
and Kawant, was how people responded to the bhouas. While surveying households and
interviewing Rathwa as well as HCPs, a surprising number of people spoke less than
highly about the practices of the local bhouas. When I asked Kadipani villagers if they
went to the bhoua when sick, many would smirk, laugh, and speak disparagingly about

these indigenous healers. This was then followed by their telling me that they do indeed
seek the services of a bhoua when sick. Regardless where I was during my field work, or
who I was speaking with, the mention of the word bhoua invariably seemed to produce
laugher, disparaging remarks, and looks of skepticism.
During one structured interview with a Rathwa 25-year-old married male and
father of two boys, I learned much about how villagers view the bhouas, a view that
seemed contradictory. When I asked this interviewee “What does the bhoua do to help
you or a family member feel better?” he quickly jumped up, went to a nearby neem tree,
broke off a branch and came back to where I was sitting. There was much laughing and
commenting among the people who had gathered to watch. Rather than just tell me his
response to my question, he was also going to show me. This respondent recruited his
mother to assist with his demonstration, with him playing the role of bhoua, she being the
patient. The man had his mother sit on the ground while he used the neem branches to
sweep her body. He also dropped some seeds over her head and around her body while
he chanted mantras. There was much laughter by those observing. I was shown how a
bhoua treats malaria, snake bite, and stomach ache, complete with an explanation of what
he was doing and why. Fortunately, I was able to video record this demonstration. I later
played the recording back for the man, that he and his family members seemed to enjoy,
laughing as they watched. While this man said he sometimes uses the services of the
bhoua, he was quick to say that he and his family also use the government clinic.

It was no different when the father-in-law and son-in-law bhouas agreed to
demonstrate their healing techniques for me. Those who had gathered around to watch,
and there were always people who were curious and wanted to see what was going on,
laughed and jeered during the demonstration. I was later told that while it is tradition for
villages to seek the healing services of the bhoua, and that they do so because they
instructed to by their elders, that many do not believe bhouas have ability to heal, but are
just cheating people for the money. Bhouas receive a fee for their healing services.
I was not sure how to interpret this phenomenon. I expected that other HCPs
might be skeptical of the healing services provided by the bhouas, but I did not expect
that the people who solicit the services of the bhoua, or those who are familiar with their
practices, to view them in a negative light. This was countered at times when an
individual believed an illness was caused by some evil spirit or malevolent god. Then,
the bhoua was revered, seen as possessing the ability to bring about divine intervention
and also a cure. While a bhoua might not be able to cure someone of malaria, he might
be able to “cure” one of a self-limited disease that runs its course and resolves on its own.
Ethnomedical Health Care Practioners Working in Kadipani and Kawant Villages
I observed 17 of the 23 ethnomedical HCPs who practiced in Kadipani and/or
Kawant. To be classified as an ethnomedical HCP, an individual had to be a bhoua, or an
Ayurvedic or homeopathic doctor. Since there was no formal list of ethnomedical HCPs
who practice in either Kadipani or Kawant, I relied on people to tell me who was a bhoua,
Ayurvedic, or homeopathic HCP and where they were located. I observed 3 bhouas who

practiced in Kadipani, 7 Ayurvedic doctors who practiced in Kawant, and 5 homeopaths
that practiced in Kawant.
Biomedical Health Care Practitioners Working in Kadipani and Kawant Villages
To be included in my participant observation of biomedical HCPs, the practitioner
had to be an allopathic/biomedical doctor who held an MBBS or MD degree. One
exception to this rule was made so as to include the medical assistant who worked at the
GMDC dispensary in Kadipani. While he did not hold a degree in either an ethnomedical
or biomedical discipline, he was included in my facility and HCP observations as he
provided a variety of biomedically-based treatments in a facility in the center of Kadipani
that was frequented by the Rathwa.
Reflections of Fieldwork
An important aspect of anthropological fieldwork is reflexivity—being able to
reflect on one’s self as well as the community one is working in. Unlike other disciplines
that study humankind, anthropology requires a certain degree of introspection. Without
this inward consideration, it would be difficult to recognize areas of potential bias,
mistakes and miscommunications, and unrealistic expectations. It is very difficult to
know or understand others, as well as their belief systems and cultural practices, if you do
not know yourself, or do not recognize what is important to you and why.
During my time in Kadipani and Kawant, I was faced with a number of situations
very different from what I might experience at home in the U.S., many of which required
me to think about who I was as a person and as an anthropologist, how I interact with
others, and how my actions may impact others’ behavior as well as their perceptions of

me. The most prominent issue I encountered in the field was being female. My gender
was the greatest impediment to my work, far greater than my language ability (or lack
thereof), skills as a researcher, or ability to endure and adapt to change and unfamiliar
environments.
Foreign Female in the Field
As a foreign female, I was instructed by many people, male and female alike, that
I should be accompanied by another person, preferably another female, at all times while
in the field. Whenever I violated this rule, I was soundly reprimanded and told not to do
it again. My translators Ankita and Hatel were both female, as was my friend Sunita,
who frequently accompanied me when I interviewed HCPs, as well as when I was
conducting participant observation in various private and public clinics and the public
hospital. I was also accompanied at times by my sponsor Dr. Vijay Shah.
I was very fortunate that a number of Indian women, including Dr. Pratyusha
Basu, my committee member, advised me on appropriate dress, etiquette, behavior when
in mixed-gender groups, and local customs. I dressed in the same style clothing as Indian
women wear (salwar, kameez, and dhupata), and I behaved in the same manner as an
Indian woman as much as possible. This greatly assisted my work. I found that people,
both men and women, were more receptive to me when I was dressed in Indian rather
than Western style clothing (Figures 9 and 10). I took a sari with me to the field, but did
not ever wear it out of fear that I could not pull off the look, style, grace, and skill
necessary to wear six meters of un-sewn fabric. I regret not having worn the sari for

some occasions. Before returning to the United States, I gave the sari to a friend who had
helped me during my stay in India.
Figure 9. Indian style dress in the field. Figure 10. Indian style dress in the field.
While I did all that I could to gain access to people in the community, I am
mindful that I probably missed out on information just because of who I am—an outsider,
a Western-educated researcher, a female, and a neophyte cultural anthropologist in a new
and unfamiliar place. I was not a neutral instrument. Regardless of how I dressed, I
never looked like the people I was studying—I am tall and have red hair, blue eyes, and
very fair skin. Once, while walking from one house to the next, my translators and I
passed a house where children were walking with small metal buckets to get water from
the hand pump. When these children, who were probably between five and ten years old,
saw me, they turned and ran, dropping their buckets, frightened by this unusual-looking
stranger! I was very cognizant of my differences and of being an outsider. I had a
difficult time feeling at ease when discussing certain topics. I avoided being alone in the

community and deferred to others when necessary, a personality trait I do not naturally
possess, and was reluctant to cultivate.
No amount of tutoring and practice could get me to the level where I could speak
Gujarati in the same way that my respondents do. I suspect that I was not privy to some,
possibly many, aspects of Rathwa culture that could have been very revealing of who
they are as a people simply because I was an outsider. When in the company of women
who were doing tasks such as caring for children, shooing chickens out of the house,
making cow dung bricks, or pumping water, I tried to participate actively. While they
frequently helped me, I was always told no, I could not help them, regardless what the
task was. At first I felt hurt, as I was being helpful or neighborly—we were all women.
It was later explained to me that I should recognize my position in the hierarchy of people
and not deviate from it. I reluctantly accepted this pronouncement.
While there were some negative aspects to being a female researcher, there were
also positive aspects. I was greeted first by females at most of the homes I visited.
Typically men were out working while women were caring for the home and children.
While I did also speak with many male informants, it was the females who invited me
into their homes, showed me around, introduced me to other family members, and spent
time talking with me about health care practices. Some women showed me their
livestock. Many women showed me their altars, and explained their daily worship
rituals. Other women showed me their children, frequently calling in those who were

playing outside, insisting they come in the house so I could see all of them lined up and
smiling.
As a woman working with two female translators I had easy access to female informants.
If I had been male, this most likely would not have been the case, and my data collection
could have been considerably more difficult.
Protection of Human Subjects
This research followed the American Anthropological Association Code of Ethics
and professional guidelines (AAA 2008), as well as the University of South Florida
(USF) Institutional Review Board (IRB) guidelines for the protection of human subjects.
These included: obtaining informed consent; maintaining confidentiality and privacy;
minimizing harm and maximizing benefits. I was forthcoming, open, and honest with all
participants as to the nature of my research. My intent with conducting this research was
thoroughly explained to all participants and informed consent was obtained before
proceeding. All participants were given the opportunity to ask questions before
participating, and were assured that their responses would remain confidential. The right
to refuse to participate was respected, as was the right to stop the survey or interview and
withdraw from participation at any time.
Summary
This chapter discussed the methods used for data collection in both Kadipani and
Kawant villages, with Rathwa adivasi as well as HCPs. The methods included informal
and formal interviews with Rathwa and HCPs, household surveys, and participant
observation in a variety of setting including individuals’ homes, the public hospital and

clinic, as well as private clinics owned and operated by allopathic, Ayurvedic, and
homeopathic doctors. This study complied with research ethics in terms of informed
consent, participant confidentiality, and security of participant data. The results of data
collection are analyzed and discussed in Chapter Six.
CHAPTER SIX
DATA ANALYSIS AND DISCUSSION
Introduction
This chapter includes my observations as a participant observer, an analysis and
discussion of the data collected from my structured interviews with ethnomedical and
biomedical health care practitioners (HCPs) who practice in Kadipani and/or Kawant
villages, and my structured interviews with a sample of Rathwa living in Kadipani
village. Also included is the analysis and discussion of Rathwa household survey data.
Data analysis includes descriptive statistics for a number of variables, and interpretative
statistics including Chi-square tests, one-way ANOVA, and multidimensional scaling
(MDS).
Participant Observation—What it Means to Be Rathwa
I was very fortunate to have been able to live among the Rathwa of Kadipani
village. The Kadipani villagers were curious about me, but somewhat more curious about
why I was curious about them. Why was I there? What was I trying to do? What I
wanted to know from them was what it means to be Rathwa.
On the day that election results for the position of Kadipani Serpunch (village
leader) were announced, I was in Kadipani collecting data. I had scheduled an interview

with the newly re-elected leader, Ramesh Rathwa, as well as his family members and other
Kadipani villagers about health, health care, and healing within the village. During all my
interviews, we sat outside in the area in front of the entryway to their homes. Typically,
other villagers who were curious about who I was and why I was there would stand around
and observe, usually remaining quite, though occasionally interjecting comments when I hit
on a topic they found compelling.
The day I met with the Serpunch was no different from any other. As usual, I was
surrounded by many people, the majority of whom were men—women and girls stayed in
the background unless asked to come forward. It was a beautiful, sunny, and comfortable
day. I was sitting on a cot typically used by the family for sleeping. A dog slept
underneath where I sat, tired from having been chased away multiple times by different
men. Chickens and other livestock passed through, unperturbed by my presence, or the
press of villagers who gradually crowded in closer, curious about who I was and why I
was there, and hoping to get a glimpse of the various electronic equipment I was hauling
about with me.
We all sat outside, next to the entrance to Ramesh’s home. The mood was festive
due to the impending grand celebration of Ramesh’s re-election. Loud, booming music
was playing, with men beating on drums and singing. I was told there was to be a victory
march through the village—and drinking, much drinking! Everyone was happy and eager
to talk. But, they also wanted me to move it along, complete my business as they had
celebrating to do. Ramesh’s mother, who frequently turned up at various homes in the
village while I was surveying and interviewing people, came towards me, introduced me

to her other children, and asked me to take a photo with her, her husband and her son, the
serpunch. She was very proud. I think this was most likely my best, most successful and
truly favorite day of field work for so many reasons.
After some casual conversation with Ramesh and his parents, congratulations to
Ramesh, including a gift of sweets to honor his success in the election (Figure 11), I
conducted a formal interview with him as well as two bhouas, father-in-law, son-in-law
pair invited to the meeting on my behalf. After the formal interviews were taken care of,
I asked the group of observers “What does it mean to be Rathwa?” There was a pause,
rapid translation of my question, silence, murmuring, and then one young man responded
in perfect English “That is a very big question!” We laughed and then talked about what
it meant to them to be Rathwa. I was told first that the Rathwa were the highest ranking
of the local adivasi, above the Bhils, the Nayaka, and other local adivasi (though they do
not have a formal caste system as that found among non-adivasi Hindus). The Rathwa
are endogamous, marrying only other Rathwa. The woman may be from a village other
than Kadipani, but she must only be Rathwa. In the words of one man “we do not send
them our daughters, nor do we take their daughter to marry our sons.”
Participant Observation—Rathwa Identity as Adivasi
I wanted to determine how the Rathwa perceived their identity as both Rathwa
and as adivasi. Group identity is influenced by a number of factors such as political
affiliation, religion, and socioeconomic status. Li notes that self-identification as
indigenous could be considered as “a positioning which draws upon historically

sedimented practices, landscapes, and repertoires of meaning, and emerges through
particular patterns of engagement and struggle” (Li 2000, 151). In the case of Indian
Figure 11. Congratulatory gift being given to newly re-elected serpunch.
adivasi, Xaxa notes that, “It has generally been assumed that tribe and caste represent two
different forms of social organization—castes being regulated by the hereditary division
of labour, hierarchy, the principle of purity and pollution, civic and religious disabilities,
etc., and tribes being characterized by the absence of the caste attributes” (Xaxa 1999,
1519).
While informally interviewing people or hanging out as a participant observer, I
frequently asked people what it meant to be Rathwa. Their answers varied, though
frequently respondents would look at me in a puzzled way. I interpreted this as their not

understanding what I was asking. I tried rephrasing the question, but still received a
shake of the head from many people. Rather than increase their puzzlement and
frustration, I moved on to other, somewhat related topics. As we sat and talked, I
attempted to get at the issue of their identity as adivasi, rather than specifically as
Rathwa. Respondents typically told me that while there were other adivasi living in
Kadipani, the Rathwa ranked higher than the other groups. Rathwa did not affiliate with
other adivasi in social events, nor was there intermarriage among the various adivasi
groups. Some respondents mentioned other adivasi they had met along the Narmada
River who were moving toward Kadipani because they had been displaced from their
homes along the river. This migration created an interesting dynamic in the Kadipani
area. There were adivasi moving toward Kadipani because they had lost their homes,
and there were non-adivasi moving into Kadipani to work for GMDC.
Since the majority of my respondents were women, it was easy to gain access to
the interior of their homes, and to talk about what was important to them and how they
lived their lives. What I found was that many Rathwa observed Hinduism to some
degree. Most homes had altars and images of Hindu deities on the walls. Women would
proudly show me their altars and demonstrate their daily worship rituals. They stressed
the importance of their spiritual beliefs and how these beliefs influenced how they lived.
I was a bit surprised that most of the images I saw were of Hindu deities. These same
women told me they visited either the Shiva temple or other temples built to honor Hindu
deities. When sick, the women or their family members would visit one of the temples,
pray and make offerings. Their spiritual beliefs were an integral part of their health care

decision making, whether praying to Shiva at the temple, or seeking the services of a
bhoua to intercede with the supernatural on their behalf. Hinduism, which is associated
with caste in India, was clearly a part of the daily lives of the Rathwa who are adivasi and
outside of the caste system.
In contrast to the observation of Hinduism, some Rathwa homes had Pithoro
images (non-Hindu deities specific to the Rathwa), either in the form of a painting on a
wall or small clay statues typically in the form of a horse. This seemed incongruous to
me, to have Hindu and non-Hindu deities in the same home. The Rathwa’s blending of
religious beliefs created confusion for me about their identity. Were they Hindu because
they recognized and worshiped Hindu deities? Were they something other than Hindu
since they also recognized and honored Pithoro deities, which are usually in the image of
a horse? Were they practicing some from of animism, which would exclude them from
being Hindu?
According to the Pew Forum on Religion and Public Life, 80 percent of Indian
nationals are Hindu (Pew Forum 2009). Adivasi typically fall outside of Hindu society
due to their lifestyle characteristics, including their religious or spiritual practices
(Baviskar 2007). I wanted to know if it was possible to be Hindu and not be part of the
caste system. I was not entirely clear who or what was shaping their religious beliefs. I
continued to ask questions about how their religious beliefs influenced their identity on
the micro level as adivasi, and on the macro level as Indian nationals. When I asked
respondents specifically about their religious affiliation, they replied they were Hindu.
Other non-adivasi informants, such as the HCPs also indicated the Rathwa were Hindu,

as did my sponsor, Dr. Vijay Shah. When I asked about the Pithoro images, the Rathwa
did not see these as separate from their Hindu beliefs and practices—they were just one
more aspect of their lives.
Participant Observation—Health Care Choices in Kadipani and Kawant Villages
Three types of ethnomedical HCPs offer services to the Rathwa in Kadipani
and/or Kawant: (1) Bhouas; (2) Ayurvedic doctors; and (3) Homeopathic doctors. I did
not meet any unani tibb practitioners, probably due to the ethnic composition of my study
area. Unani is primarily practiced by Moslem healers; there were few Moslems in the
Kawant and Kadipani communities.
The Rathwa have a variety of options for treating and preventing sickness.
Biomedical HCPs are available in both Kadipani (a medical assistant at the GMDC
dispensary) and Kawant (a biomedical physician at the government clinic and hospital).
The HCPs that people access could begin with a visit to a local traditional healer, then
possibly follow a winding course from ethnomedical practitioners to biomedical
practitioners, sometimes weaving back and forth with the health care service recipient
utilizing different services or providers when treatment does not progress as desired, fails
entirely, or appears to be caused by “other-than-human entities” (Garro 2000).
Participant Observation—Rathwa Beliefs
Indigenous healers have long played a significant part in both the physical and
mental health of many populations. Of concern is how indigenous or ethnomedical
healers interface or collaborate with biomedical healers in the care of the sick, especially
those with serious illnesses or infectious diseases. Unfortunately, many adivasi

communities are “facing extinction due to endemic diseases” (S. Basu 1992:14), a
problem that frequently could be prevented by the provision of adequate health care
services that not only include treatment as well as prevention programs, but that
recognizes the role of indigenous healers in their communities and strives to include them
in health care provision and planning when appropriate.
Rathwa health care decision making is based on beliefs about what causes illness
and how best to cure that illness. For the Rathwa, bhouas are folk medicine practitioners,
using their abilities to intervene on behalf of the patient with the supernatural. Since
many Rathwa believe that sickness or disease are caused by evil spirits, malevolent gods,
or some other misfortune, the role of the bhoua is important to the well-being of the
community for a variety of reasons. While in Kadipani, I was told that bhouas are also
referred to as “practitioners of the black arts,” as they have the ability to remove ghosts
and dispel curses.
Recognizing that all cultures may have some form of folk illness, and that beliefs
about what causes sickness and disease are variable, it follows that Rathwa concepts
about what makes people get sick would influence their health care decision making.
During my structured interviews with the Rathwa, I found that many people believed
certain maladies to be better suited to the healing techniques of a bhoua, such as
headaches and snake bites. Frequently, respondents would tell me they always go to the
bhoua, no matter what their illness. If they do not achieve relief from their symptoms
after a session with the bhoua, then they try another treatment option with some other

HCP. Interestingly, it is the bhoua who tells the sick person to go to a doctor after
administering a treatment then.
Participant Observation—Gods, Healing, and Art
While working in Kadipani, I spent much time with people at their homes. I was
typically invited inside to see their babies, their livestock (which are penned in the home)
and, on occasion, Pithoro paintings. Pithoro paintings, which have a very specific
purpose in the lives of the Rathwa, especially as they relate to sickness and health, have
been researched by Vishrajit Pandya (Pandya 2004), who has examined the role of
Pithoro paintings in the lives of Rathwa experiencing suffering or misfortune. While
visiting with villagers in their homes, I saw several Pithoro paintings, some newer, some
older, some in homes of those who appeared wealthier than others. All covered an entire
wall in the main area of the house, and were a source of pride for the occupants.
Residents typically invited me to examine the paintings closely and take photos of them
standing next to the painting.
I had read about these painting prior to my leaving for the field, so I was on the
lookout for them. I was ecstatic the first time I entered a house that had such a work, and
I encouraged the owner to speak at length about the painting and its significance to the
family. After viewing a few of these paintings, I noticed themes found in all of them.
Artistically, all of the Pithoro paintings had a white background with a variety of figures
positioned about the work, all in different colors, though mostly blue and dark pink or
red. These are water-based paints made from plants to create color, with a bamboo stick
used as a brush. The painter, who is commissioned by the family and compensated for

his work, is known throughout the village, as this is a community process, one that
involves a puja (religious ritual), food, and typically two days of ceremony. Each
painting had figures of horses, which is very significant, as horses represent Pithoro, a
god. There were also figures of people doing work and/or leisure related activities, as
well as other animals. I was told these figures represent what is going on in the
community, though the people who live in the home are not represented in the painting.
The painting itself is considered a god, therefore it is to be treated with reverence
and respect, with obligations incurred. A number of people are involved in the creation
of a Pithoro painting once a household decides to commission one. First is the Lekhar,
the man who paints or writes the painting, one who is respected throughout the village
for his work. Second is the Badvo, who interprets or divines the painting, typically
indicating that Ind and Pithoro (divinities) have vacated the home and thus misfortune
has ensued (Pandya 2004:123).
Residents of all of the homes I visited with Pithoro paintings indicated that they
had suffered some form of misfortune, most frequently poor health by a family member,
and were prompted by this misfortune to commission a painting. One household I
surveyed that was located on the top of hill with a panoramic view had commissioned
their Pithoro painting (Figure 12) when their eldest male child contracted tuberculosis
(TB) when he was three years old. The head of the household/father of the boy was very
proud of the painting, and asked me to examine it closely and to take a picture of him
standing beside it. He also asked me to spend time with his son, whose TB had
progressed to his brain, and was in a semi-vegetative state.

On the day of my visit, the boy, who was now 16 years old, was outside in the
sunshine lying on a cot, wrapped in a quilt, under the supervision and care of his eldest
Figure 12. Pithoro painting in a home in Kadipani village.
sister. This family truly loved this child and asked what I could do to facilitate his
recovery. They had sought treatment from many ethnomedical and biomedical health
care service providers, going as far away as Ahmadabad, trying to heal their son. The
Pithoro painting was one aspect, a spiritual aspect, of their healing quest. After spending
some time with the family, we completed a household survey, and I then interviewed the
head of the household, who told me about his Pithoro painting.
After the formal aspects of my work were complete, we all sat outside talking.
Various family members encouraged the boy to open his eyes so he could meet me. They

also seemed to desire some type of divine intervention by me on his behalf. My translator
asked “Ma’am, they want to know what you can do to help the boy, to make him better?”
The family had gone to what I consider great lengths, including traveling extremely far
from home, to find a cure for their son. All I could I offer was to spend time with them,
talking about their life together as a family. Interestingly, one advantage this family had
over many others was that the father worked as a welder for GMDC. Thus, not only did
the family have a monthly income that supplemented farming, but they also had a health
care benefit that exceeded that of someone who does not work for GMDC.
Participant Observation—Bhouas
I observed three bhouas (all males) who were all Rathwa adivasi living in
Kadipani. These men were primarily farmers, but also practiced as bhouas, having come
to that role for a variety of reasons. Their approach to healing may vary, with some using
chanting and prayers, others using plants to sweep illness out of the person or as a formal
treatment modality, as is the case with neem for treating fever. Still others may go into a
trance-like state, calling on the divine for intervention, which could include not just
healing but also predictions for the future.
Three bhouas from Kadipani village were interviewed. No one could tell me how
many bhouas live and practice in Kadipani. I was told that: (1) anyone can be a bhoua;
(2) they are all men; and (3) while they may live in Kadipani, they may also move about
the local area practicing their healing, rather than staying in one place like other HCPs,
such as those who have clinics in Kawant. I was informed of who was a bhoua by the
Kadipani serpunch, as well as by other people living in Kadipani. The village serpunch

provided me with access to the three bhouas I interviewed. I interviewed only those
bhouas living in Kadipani, as I was told the Rathwa of Kadipani seek the services of
bhouas of Kadipani.
While I have been told “anyone can be a bhoua,” it is also considered by many,
especially the bhouas I spoke with, to be a calling. This calling is typically attributed to
divine intervention in that a god or goddess comes to the person in a dream and instructs
him to become a bhoua. Bhouas believe they have supernatural powers that facilitate
their ability to bring about healing, a detail they revealed to me during my interviews.
Those Rathwa seeking the services of a bhoua also believe this. Two bhouas stated they
were self taught, relying on divine intervention to guide their practices, and one said he
was trained by his father in law. When I asked anyone—villagers, HCPs, whomever—
what it meant to be a bhoua, the responses I received most frequently were: (1) a
practitioner of the black arts; and (2) a remover of ghosts.
The first bhoua I observed was 45 years old, had been practicing for about 15
years, was married and had eight children, one of whom had died. This bhoua not only
treated various illnesses such as malaria, snake bites, and diarrhea, but also had divinatory
skills which he used for “diagnosing” illnesses and for predicting the future of his
patients. His practice entailed moving around the countryside providing healing to those
in need, worshiping at temples, and praying in seclusion. When asked, he stated that no
one taught him to be a bhoua. Instead, he recounted a story of how when he was visiting
an old, small temple, gods and goddesses appeared to him and instructed him to become a
bhoua. They gave him the energy and supernatural power to do this work. This first

bhoua demonstrated how he treats illnesses. He started his demonstration of healing by
laying a small mat on the ground. He used seeds and kesuda leaves in his divinatory
work, speaking softly, shaking seeds from his hand, and making interpretations.
The other two bhouas I observed were a father-in-law and son-in-law who were
brought to me together while I was visiting the house of the Kadipani serpunch. The
father-in-law was 70 years old and frail, carrying a large walking stick, his head wrapped
in a white scarf. He told me he was the oldest person in Kadipani village and that he had
been practicing as a bhoua for a long time, about 45 years. He said he was self trained
and that he had been directed by the gods to do this work. This elderly bhoua then
introduced me to his son-in-law, who he had personally trained in the practice of the art
of healing.
The son-in-law told me he was about 55 years old, that he had been practicing as
a bhoua about 25 years, that he uses traditional medicinal plants to treat headache and
abdominal pain, and that he also delivers babies. Fortunately, he was willing to
demonstrate for me how he treats malaria. This demonstration included the use of leafy
branches torn from a neem tree to sweep the body of the person who is sick, all while he
and his father-in-law loudly chanted mantras, calling on the Hindu deity Krishna for
divine intervention to heal the patient.
Participant Observation—Ayurvedic and Homeopathic Practitioners
I observed seven Ayurvedic doctors and five homeopathic doctors practicing in
Kawant. As mentioned, there were no unani tibb practitioners in either Kadipani or
Kawant. Each Ayurvedic or homeopathic doctor had his or her own private clinic where

they saw patients for a wide variety of maladies. Two of these HCPs were women, 10 were
men. Their private clinics were typically small store fronts where patients seeking
treatment could just walk in and be seen. These private clinics seemed to be clustered
primarily in two areas, the first being where the main road comes into Kawant—a
commercial area, the hub of activity where busses stop, trucks make deliveries, and lots of
people and animals were present. This is a noisy, bustling commercial rather than
residential area. I found many clinic store fronts in this area and would walk from one to
the next, visiting, observing and interviewing HCPs. These clinics were small, typically
one room with a curtained-off area where patients could be examined. The HCP would sit
at a desk waiting for patients.
The second area in Kawant where private clinics were found was toward the
center of the village, the same area where the haat (local market) is held every Monday,
near homes and smalls businesses alike. This was a quieter area with more personality
than the commercial area. I truly enjoyed this part of Kawant because of its numerous
small shops selling everything from household utensils, clothing, traditional adivasi silver
jewelry, and spices. It looked interesting, it smelled like spices—as I imagined India
would smell, and the people were willing to talk. Here the clinics were a bit larger,
having more than one room, and the HCP’s practices might include an area of
specialization.
During my periods of participant observation in these private clinics I consistently
observed the same thing—people who were not trained as allopaths practicing allopathic
medicine. Also, while conducting structured interviews with these same HCP, when

asked “What type of health care do you provide?”, for which there were six closed
responses they could chose from, before I could even give the interviewee the first
response choice, practically everyone said “allopathy.”
Only one allopath interviewed and observed was trained and educated to practice
allopathy in Kadipani or Kawant, but numerous ethnomedical HCPs claimed to practice
biomedicine, including taking x-rays, prescribing medications, giving injections, suturing
wounds, and placing casts on broken bones. I discussed my concern about non-allopathic
doctors practicing allopathy with Dr. Vijay Shah, my sponsor who is a trained allopathic
physician. We talked about possible explanations for this, such as the shortage of
allopathic doctors working in rural areas; the pressing need for allopathic medicine and
biomedical treatment modalities; and the demands of patients. As was relayed to me
repeatedly during interviews with HCPs, patients frequently come to see an HCP to
request a specific form of treatment. The allopathic doctor told me that the Rathwa are
particularly fond of receiving injections and will specifically ask for such even if it is not
medically warranted.
I considered how this behavior of non-allopaths practicing allopathy might relate
to the development of health-related policy in India. HCPs in India are monitored by the
Indian government. Only allopaths should be practicing allopathy, but there is little done
to address the issue of non-allopaths practicing allopathy for a number of reasons, not the
least of which is the increasing need for the provision of such services caused by factors
such as a burgeoning population, as well as government-designated population health
goals or standards.

Participant Observation—Allopathic Practitioners
I observed two biomedical HCPs in the facilities where they worked. One of
these was an allopathic doctor who worked for both the public clinic and public hospital
in Kawant, facilities that are located within the same compound. In addition, this allopath
also had his own private clinic in Kawant, where he typically worked in the afternoons,
working at the public clinic and hospital in the morning and in the evening. The other
biomedical HCP was a medical assistant who worked for the GMDC-sponsored
dispensary in Kadipani. Though he did not hold a MBBS or MD degree, this medical
assistant had been trained in biomedical treatment methods and had been treating patients
for 35 years using allopathic/biomedical methods such as giving inoculations, treating
snakebites, suturing wounds, taking x-rays and placing casts on broken bones, giving
medications, etc. He specifically stated that he does not deliver babies, and that extreme
cases are referred to the allopathic doctor in Kawant.
It was quiet during my visit to the GMDC dispensary. One patient was just
leaving as I was arriving, and people occasionally trickled in during my time observing.
The medical assistant gave me a tour of his facility (Figure 13), and we talked about the
types of cases he typically sees on a given day, focusing on how many Rathwa from
Kadipani he might see. He explained that GMDC sponsored the dispensary and that all
services were provided free of charge. He also works with a “nurse” or “sister” as he
referred to her, who had a variety of health care-related duties including working with
women, especially those who were pregnant, including prenatal and post natal care.

Figure 13. Medical assistant at GMDC-sponsored clinic in Kadipani.
The medical assistant told me he has a general practice, treating just about
anything that patients present, including stitches, casting of broken bones, taking x-rays,
and various other needs. He lives near the dispensary in GMDC housing and may come
to the dispensary during the night if there is an emergency. On the day of my visit he
saw 19 patients for a variety of issues. He does see patients for malaria, but refers people
in sickle cell crisis to the allopathic physician at the public clinic/hospital in Kawant, or
if the patient has money for medical care, he refers them to health care facilities in
Baroda, a city about 2 hours drive from Kadipani.
The other biomedical HCP included in my participant observation was Dr. P., the
only allopath working as a clinician at both the government clinic and hospital

(Figure 14) in Kawant. Dr. P. was very accommodating. He invited me to see all that there
was to see in both the public clinic and public hospital, both very busy places seeing to the
needs of anyone form the surrounding villages. As the only allopath in the area Dr. P. sees
a wide variety of cases, many of which are severe or critical, having been referred to him
by other HCPs in the area who are not able or equipped to deal with serious health-related
problems. Dr. P. lives in a small residence within the government health care compound
and is available “all the time” round the clock, according to him. This makes Dr. P. a very
busy man. Dr. P spent a considerable amount of time with me during my stay in Kadipani
and my observations in Kawant. To show my gratitude, I gave various medical items (latex
glove, alcohol swaps, antibacterial hand cleaner, etc.) to Dr. P.
Figure 14. Government hospital in Kawant.

My first day of observation at the public clinic included Dr. P. and I seeing 15
patients with a variety of maladies in just a couple of hours. Patients were male and
female, young and old, acutely or chronically ill, and very cooperative. They were quiet
and soft spoken, forming a line at the doorway to the examine room which extended into
the hall. I enjoyed participant observation at the public clinic, as it was so busy. I got to
meet many people, all curious about who I was, some mothers wanting to show me their
babies, others thinking I could offer some “American style” medicine that could provide a
cure to a long standing malady, such as the resolution of a chronic ulcer on the ankle of a
boy who had a club foot.
One interesting case, a 23-year-old married woman with a year-old baby,
illustrated the intersection of ethnomedical and biomedical health care practices among
the Rathwa. This young woman came to the public clinic complaining of severe pain and
swelling in her right breast. She was still breastfeeding her baby, and according to Dr. P.
she had mastitis, a condition common in nursing mothers and easily treated. Prior to
coming to see Dr. P., this woman had gone to see a bhoua in the village for the same
condition. She saw this same bhoua 7 times in 7 days. She had no relief from her
symptoms and found her condition worsening.
Dr. P. diagnosed the problem and prescribed an oral antibiotic and pain
medication. The woman appeared relieved and left the clinic. When I saw her days later,
she was happy and relieved, healthy again. This woman believed in the healing power of
the bhoua, and went to see him repeatedly because she was instructed to do so by her
mother-in-law. When her illness began to interfere with her ability to care for her home

and family, she sought the services available at the government clinic, which were free.
The services of the bhoua cost money, even if just 20 or 30 rupees, which can add up
over the course of a week, and seem like money wasted when one does not get better.
Toward the end of our clinic hours on my first day of observation, a family carried
in an elderly man wrapped in a blanket and laid him on a bench outside the examination
room. The patient was experiencing severe chest pain, and Dr. P. said he was in cardiac
arrest. The patient, referred to as Kaa Kaa (uncle), was admitted to the hospital, where
he was placed in a bed, had an IV inserted into his arm, and was monitored periodically.
Later that morning, I stopped in to see how Kaa Kaa was doing. He was unresponsive
with labored breathing and had vomited on his shirt. Kaa Kaa was surrounded by his
family, who looked quite worried. Later that same day, before I left Kawant, I stopped in
again to check on Kaa Kaa. He was no longer in the hospital. Dr. P. told me the family
took him home to die.
I also visited with a number of other patients in the hospital wards that day,
including a young woman and her father who had brought her into the hospital due to
her experiencing sickle cell crisis symptoms; a man who had eaten poison in a suicide
attempt after an argument with his wife; a man who had been beaten by someone he had
a dispute with; and a man who had been chopped in the leg with an axe by another man
during a fight.
I spoke at length with a young woman with sickle cell disease. Her father told me
(with Dr. P. translating) that the woman’s husband had “expelled” her from their home.

Due to the severe symptoms of sickle cell crisis that she was experiencing (joint pain,
dizziness, inability to stand or walk) she was unable to carry out her household duties. Her
husband, not knowing about sickle cell disease or crisis, thought that the woman was just
being lazy and he put her out. The woman returned to the home of her father, who brought
her into the hospital. She was lying in bed, had an IV in her arm, and was receiving
analgesics for her pain. Dr. P. speculated that she would be released later that day. Perhaps
if her husband had known she had sickle cell disease, and what the symptoms are when
someone is in sickle cell crisis, he might have been more sympathetic toward her condition.
I cover this issue in greater detail in Chapter Eight when I discuss recommendations, follow
up research, and education programs.
In another ward of the hospital, I spoke with a new mother and her mother-in-law.
The new mother was 19 and had just given birth not an hour before to her first baby, a
son. The baby was premature and had low birth weight. In spite of repeated efforts by
the new mother, the baby would not nurse—he would not even respond. This was the
smallest baby I have ever seen. Dr. P. told me that his chances of survival were not good
due to his prematurity, low birth weight, and the fact that he was not nursing, and it was
very cold. This was January and the temperature, especially at night, was very low. I did
not see that young mother again during my fieldwork, so I do not know what happened
with her newborn son after I saw them in the hospital.
Participation Observation—Rathwa Perceptions of Health Care Practices
What I noticed most while observing the HCPs in their respective facilities was
that, while indigenous/folk medicine practitioners continue to provide health and

healingrelated services to the Rathwa, the view of these practitioners by fellow villagers
appears to be changing. During my time interviewing villagers and surveying households,
they shared their opinions about the quality of services they have received from various
public and private HCPs, ethnomedical and biomedical alike, as well as why they seek the
services of certain providers over others.
While the severity of an illness and the cost of health care services were critical
factors in household health care decision making, people were also influenced by the
direction of their elders and long-standing cultural practices, as well as personal and
group belief systems. Choosing to seek the services of a biomedical rather than an
ethnomedical health care practitioner may be in response to different factors, such as was
the case with the young mother with mastitis. Her symptoms did not improve after seven
visits to the bhoua; her decision to go to the public clinic was prompted by cost, since she
had all ready paid him seven times. The public clinic was free. For the mother with the
premature, low birth weight, newborn son, institutional delivery was the wisest option,
since the baby was coming early and it was her first delivery.
Deshora (1995) notes that across India there is concern about a growing
imbalance in the male/female ratio, because of selective abortion, and the status of
females is significantly lower in tribal and non-tribal communities. I considered how this
might translate into differential access to health care systems. During my preliminary
visit in June 2007, the medical director at the public hospital informed me that the Indian
government was encouraging hospital delivery of babies instead of home births with the
assistance of traditional birth attendants. During an interview with a traditional birth

attendant, the woman seemed to be telling me what she thought I wanted to hear. While
she had worked as a traditional birth attendant for years, recently she had attended a
government-sponsored class on delivering babies. Rather than telling me what she
traditionally would do to facilitate the birth process, she told me what the government had
instructed her to do as a birth attendant. This made it difficult for me to learn what had
been practiced in the past, but also made building rapport difficult, as the woman
appeared to fear going against what the government had taught her.
Recognizing that “culture affects our perceptions and experiences of health and
illness in many ways, and these perceptions and experiences change as culture changes”
(Loustaunau and Sobo 1997:17), it follows that as the Indian government introduces
health care systems and practices that differ from those traditionally practiced among
adivasi groups, there may be a clash between tradition and modernity, disparity in power,
and changes in cultural practices, especially as they relate to long-practiced indigenous/
folk/ethnomedicine and rapidly developing biomedical practices.
Participant Observation—Some People Do Speak English!
Early one day during my time in Kadipani, I ventured out by myself. My
translators, who were college students on a brief break from their schooling, were
reviewing their studies for upcoming exams, and needed time for that work. That day, I
planned to meet with the medical assistant who worked at the GMDC dispensary in the
center of Kadipani. I had met this medical assistant during my preliminary visit in June
and had spoken with him in English, so I was confident I could do so again this day. I
walked by myself from the GMDC guest house to the dispensary. Along the way I passed a

number of people who looked my way; some acknowledged me, while others just watched
me walk by.
I arrived at the GMDC dispensary and introduced myself to the medical assistant
who runs the facility. After some small talk and a tour of the facility, we began the
interview. When I was ready to leave, the medical assistant suggested I walk across the
road to see the local primary school and the GMDC employee housing complex. I took
his advice and walked toward the housing complex. On my way, a man drove up on his
motorbike, stopped, and spoke to me in English, asking why I was there and what I was
doing. We spoke briefly—he told me a bit about the area and invited me to visit him at
his home sometime. I thanked him and went on my way.
As I proceeded back to the GMDC guesthouse, I was stopped again by another
man who called to me in English and motioned for me to come to where he was sitting at
the building next to the Shiva temple. I approached, somewhat skeptical and wary. The
man spoke excellent English. He said he saw me walk by earlier and wondered who I
was and what I was doing. We talked outside the entrance to the building, and he then
invited me inside. The building was the living quarters for the Hindu priest who ran the
Shiva temple, as well as guest quarters for visiting sadhus (Hindu holy men).
Bearing in mind that I was an unaccompanied female, and that I was entering
living quarters for men, I became apprehensive. Inside were four men, one of them the
priest from the Shiva temple. I had met this priest on two prior occasions, the first during
my preliminary visit in June when I unknowingly entered the temple during a time when
only men were allowed; and the second when my translator and I visited during a worship

service. This priest spoke a little English and we chatted briefly about my stay in the
village.
The other three men, all of whom had varying degrees of English fluency, told me
they were traveling sadhus, in the area because they were circumambulating (walking
around) the perimeter of the Narmada River, one of the seven most holy rivers in India.
Walking the perimeter of the Narmada River is considered a meritorious act, a way of
showing reverence for the goddess Narmada. We talked at length about why they were
walking around the Narmada River (worship), how long it would take (approximately two
years), and the total distance they would be walking (2,600km). The sadhus asked about
my project and how I liked living in India. I was invited to have lunch with them.
In addition to my previously being instructed by a number of people to not travel
anywhere alone, I was also told not to eat or drink anything offered to me while in the
village, but for food and water at the GMDC guesthouse. Now I had a dilemma on my
hands. I had just received an extensive lecture on the power of the goddess of the
Narmada River. One sadhu told me she protects him on his travels, and that she had
manifested me to him so he could speak to someone, in English, about his trek. To refuse
to have lunch with these men would have invalidated what they believe—that the
goddess Narmada would protect us all. At first I politely declined, saying that I had left
my translators behind at the guesthouse, much time had passed since I left that morning,
and that people would begin to worry. Again, I was told by the sadhus that the goddess
meant for me to be there. I finally accepted their invitation and we moved into another

room for lunch, sitting on the floor and eating with our hands food that was absolutely
delicious.
After we had finished our food, I took my leave, thanking them for their
hospitality and saying good-bye. I walked back to the GMDC guesthouse where upon
my return I was immediately quizzed at length by my translators as to where I had been,
what I had been doing, and who I had been with. They were stunned when I relayed to
them my morning activities. Why would I do such a thing? They eyed me suspiciously
and returned to their studies while I went to my room to write field notes. Lingering in
the back of my mind were thoughts about whether or not I would get sick, having eaten
food I was instructed not to eat. No, I did not get sick, and it was some of the best food I
ate while in India. When I told Dr. Vijay about this experience, he looked at me and said,
“of course you didn’t get sick.” That I met six people in less than two hours who all
spoke English was also intriguing. Such an experience could not have been planned.
Structured Interviews with Ethnomedical and Biomedical Health Care Providers
Structured interviews consisting of open and closed-response questions were
conducted with 20 ethnomedical and biomedical HCPs in both the public and private
health care sectors. These HCPs practice in either Kadipani (n = 5, 25 percent) or
Kawant (n = 15, 75 percent) villages. Most of the non-bhoua HCPs (n = 16) spoke some
English, with a number being fluent. Translators accompanied me to my interviews and
would translate or explain confusing words or concepts. All interviews were voice
recorded, and photos were taken of each HCP and his/her clinic/work location if they so
agreed.

To be considered an HCP, and to be eligible for inclusion in this study, the
practitioner had to be a bhoua, or an Ayurvedic, homeopathic, or allopathic/biomedical
doctor. One medical assistant who had been trained in allopathy had 35 years experience in
the field, and who worked at the local dispensary in Kadipani, was included in the data
collection. He provides a wide array of services for the Rathwa, and the dispensary where
he works is located in the center of Kadipani village. The services provided at this
dispensary are free, as it is sponsored by GMDC, which is just a short distance up the road,
and easily accessible by the Rathwa. A female traditional birth attendant who was Rathwa
and lived in Kadipani was also included in my analysis.
Of the 20 HCPs interviewed, 85 percent were male (n = 17) and 15 percent were
female (n = 3) (Figure 15). The HCPs ranged in age from 24 to 70, with the mean age
being 39 and the median age 37. There was a tri-modal distribution by age, with peaks at
28, 30, and 37 years (Figure 16).
When asked “Do you have an area of specialization?” 25 percent (n = 5) replied
yes, and 75 percent (n = 15) replied no (Figure 17). One allopath stated he specialized in
public health, having had 14 years in the field. An Ayurvedic practitioner explained that
he specialized in the treatment of proctological cases, using thread medicated with
Ayurvedic herbs to tie off and remove hemorrhoids. One bhoua said he specializes in the
treatment of headache and abdominal pain, treating these ailments with locally available
medicinal herbs, and another bhoua said he specializes in the treatment of neck and
shoulder muscle strains. The traditional birth attendant only delivers babies.
The remaining HCPs stated they were general practitioners, seeing a wide variety
of cases in their clinics. All noted that some conditions are seasonal, such as an increase
in the number of snake bites and malaria cases during monsoon season. Snake bites
Figure 15. HCP distribution by gender.
increase when people are outside more, preparing their fields for planting. When it rains,
there is standing water where mosquitoes breed and proliferate, and people are
increasingly at risk for bites by the female anopheles mosquito that carries the parasite
that causes malaria.
Both HCPs affiliated with the government-run public clinic and hospital in Kawant
(n = 2) were interviewed. This included the block health officer who oversees operations at
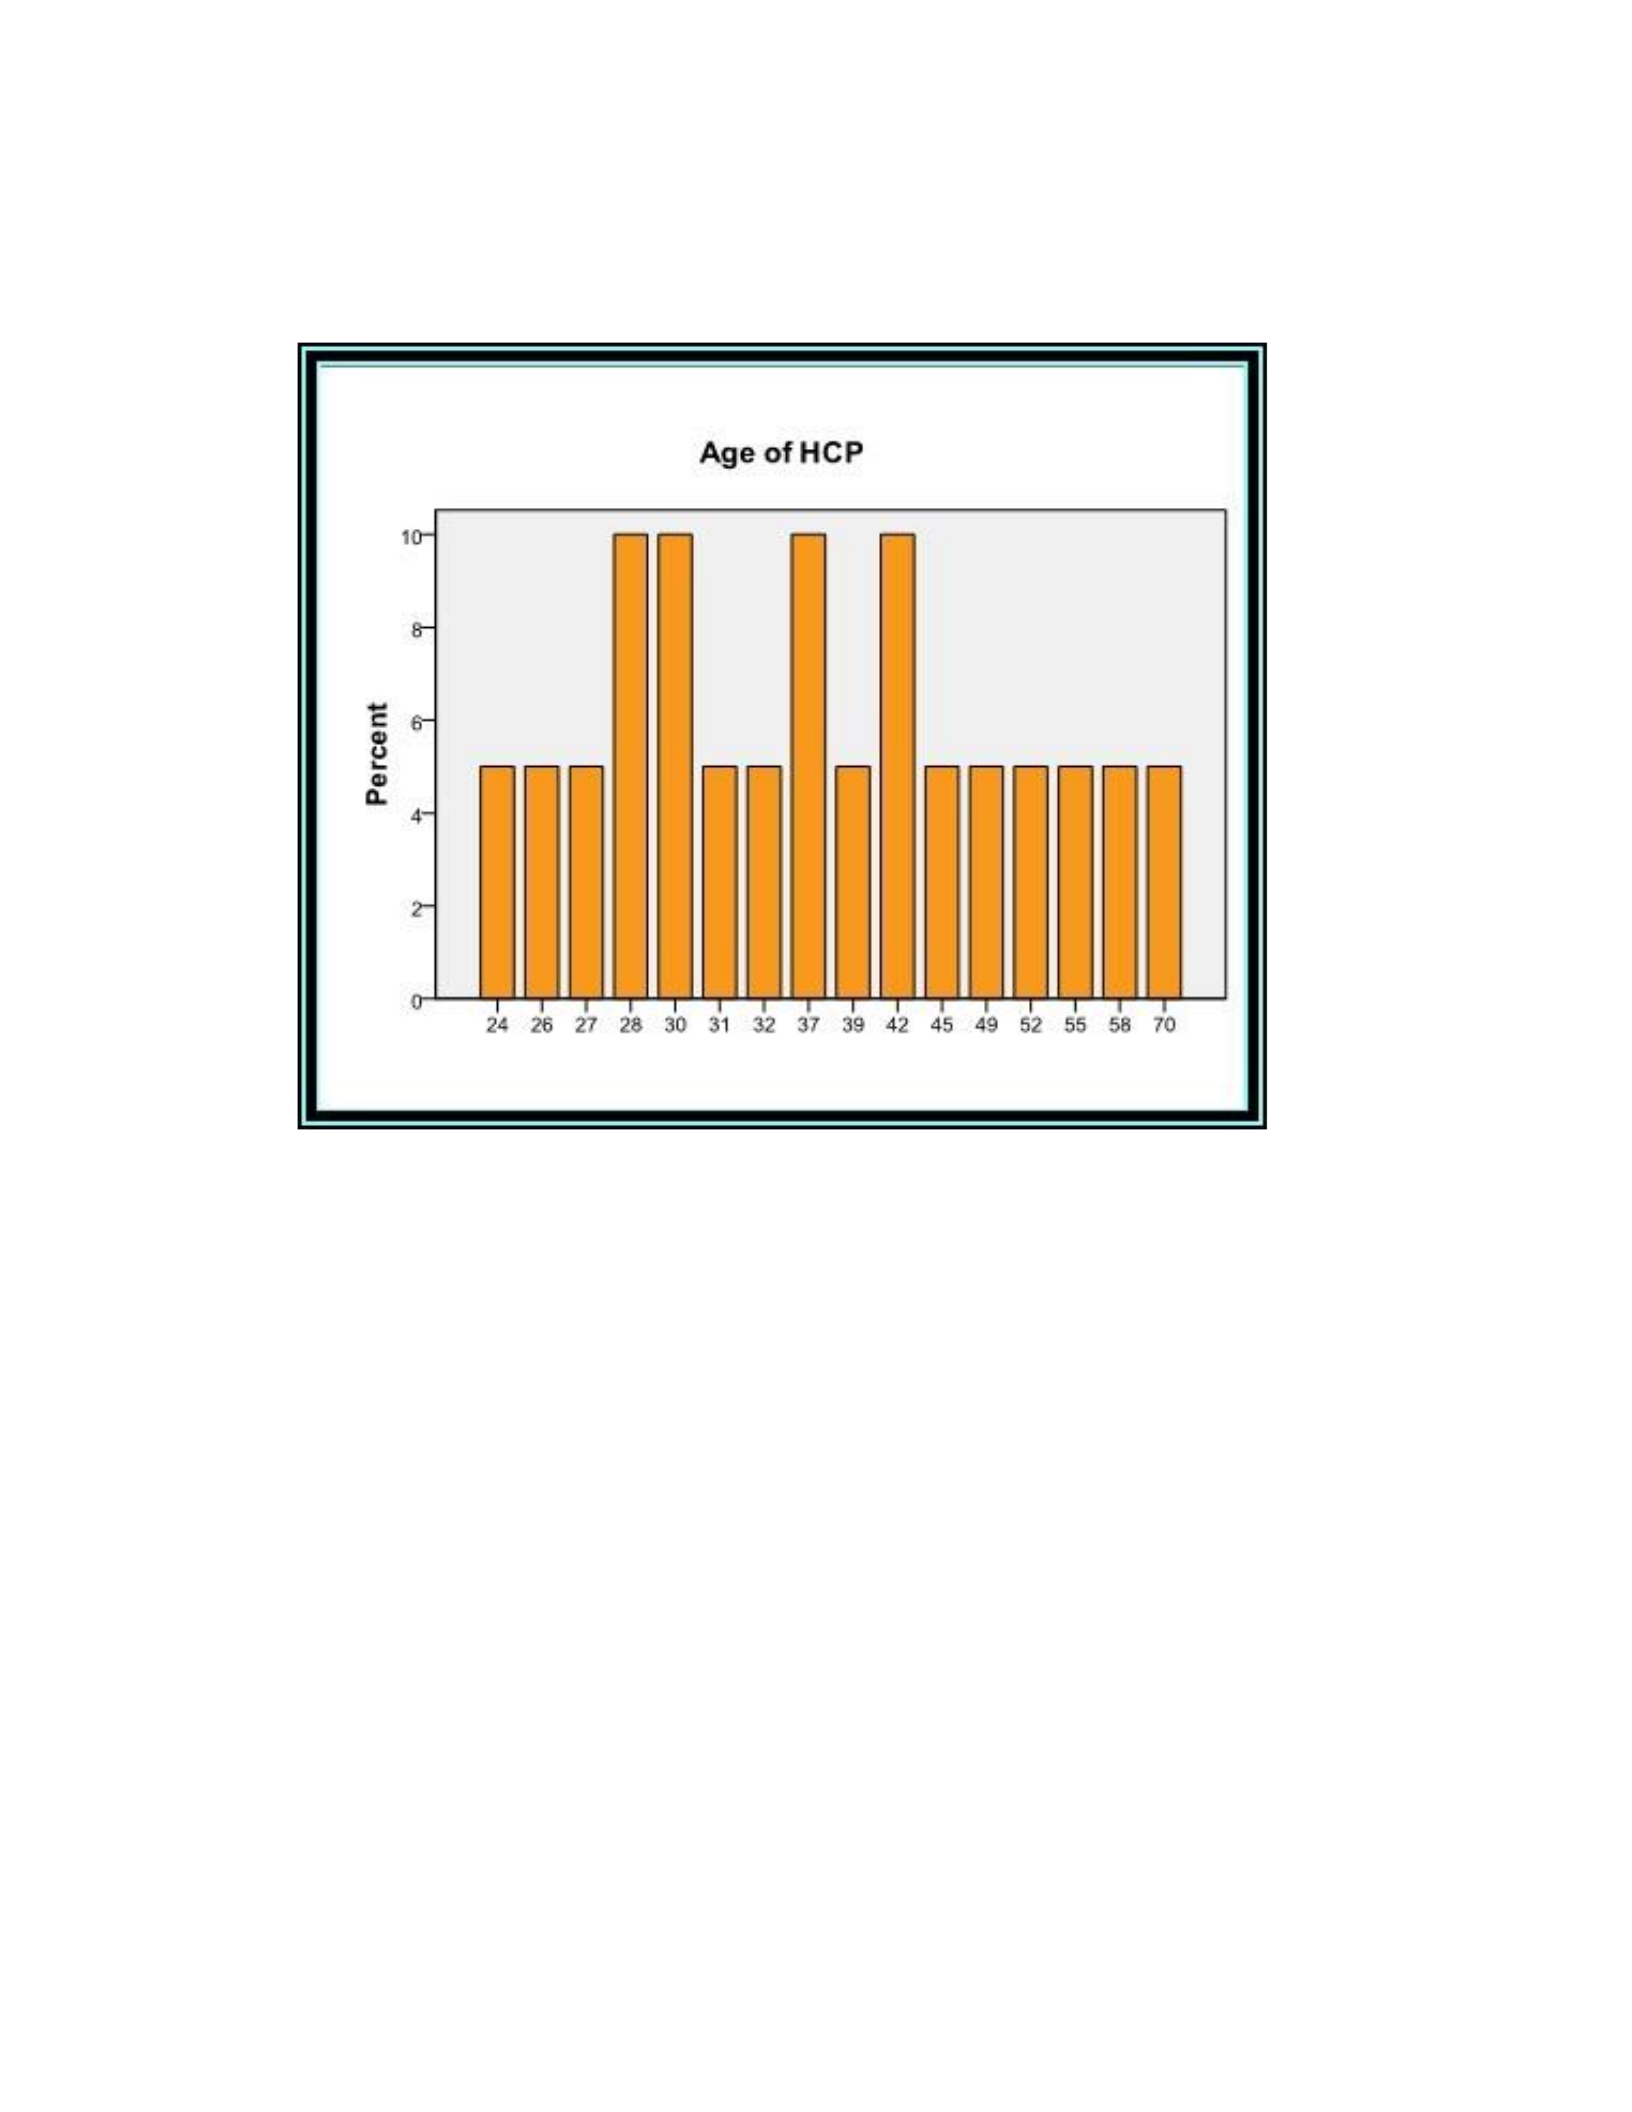
both the clinic and hospital, and the physician who daily treats patients in both the clinic
and the hospital. Both these HCPs were allopathic/biomedical doctors holding MBBS
Figure 16. HCP distribution by age.
degrees from medical colleges in India. Each had considerable experience in the provision
of health care services for adivasi groups.
During my structured interviews, when asked “What type of health care service do
you provide?” 15 percent (n = 3) responded “Allopathic/Biomedical,” 40 percent (n = 8)
responded “Ayurvedic”, 25 percent (n = 5) responded “Homeopathic”, 15 percent (n = 3),
identified as bhouas, and 5 percent (n = 1) indicated “Other” (Figure 18). Interestingly, all
HCPs, except the bhouas and the traditional birth attendant, told me that they practice
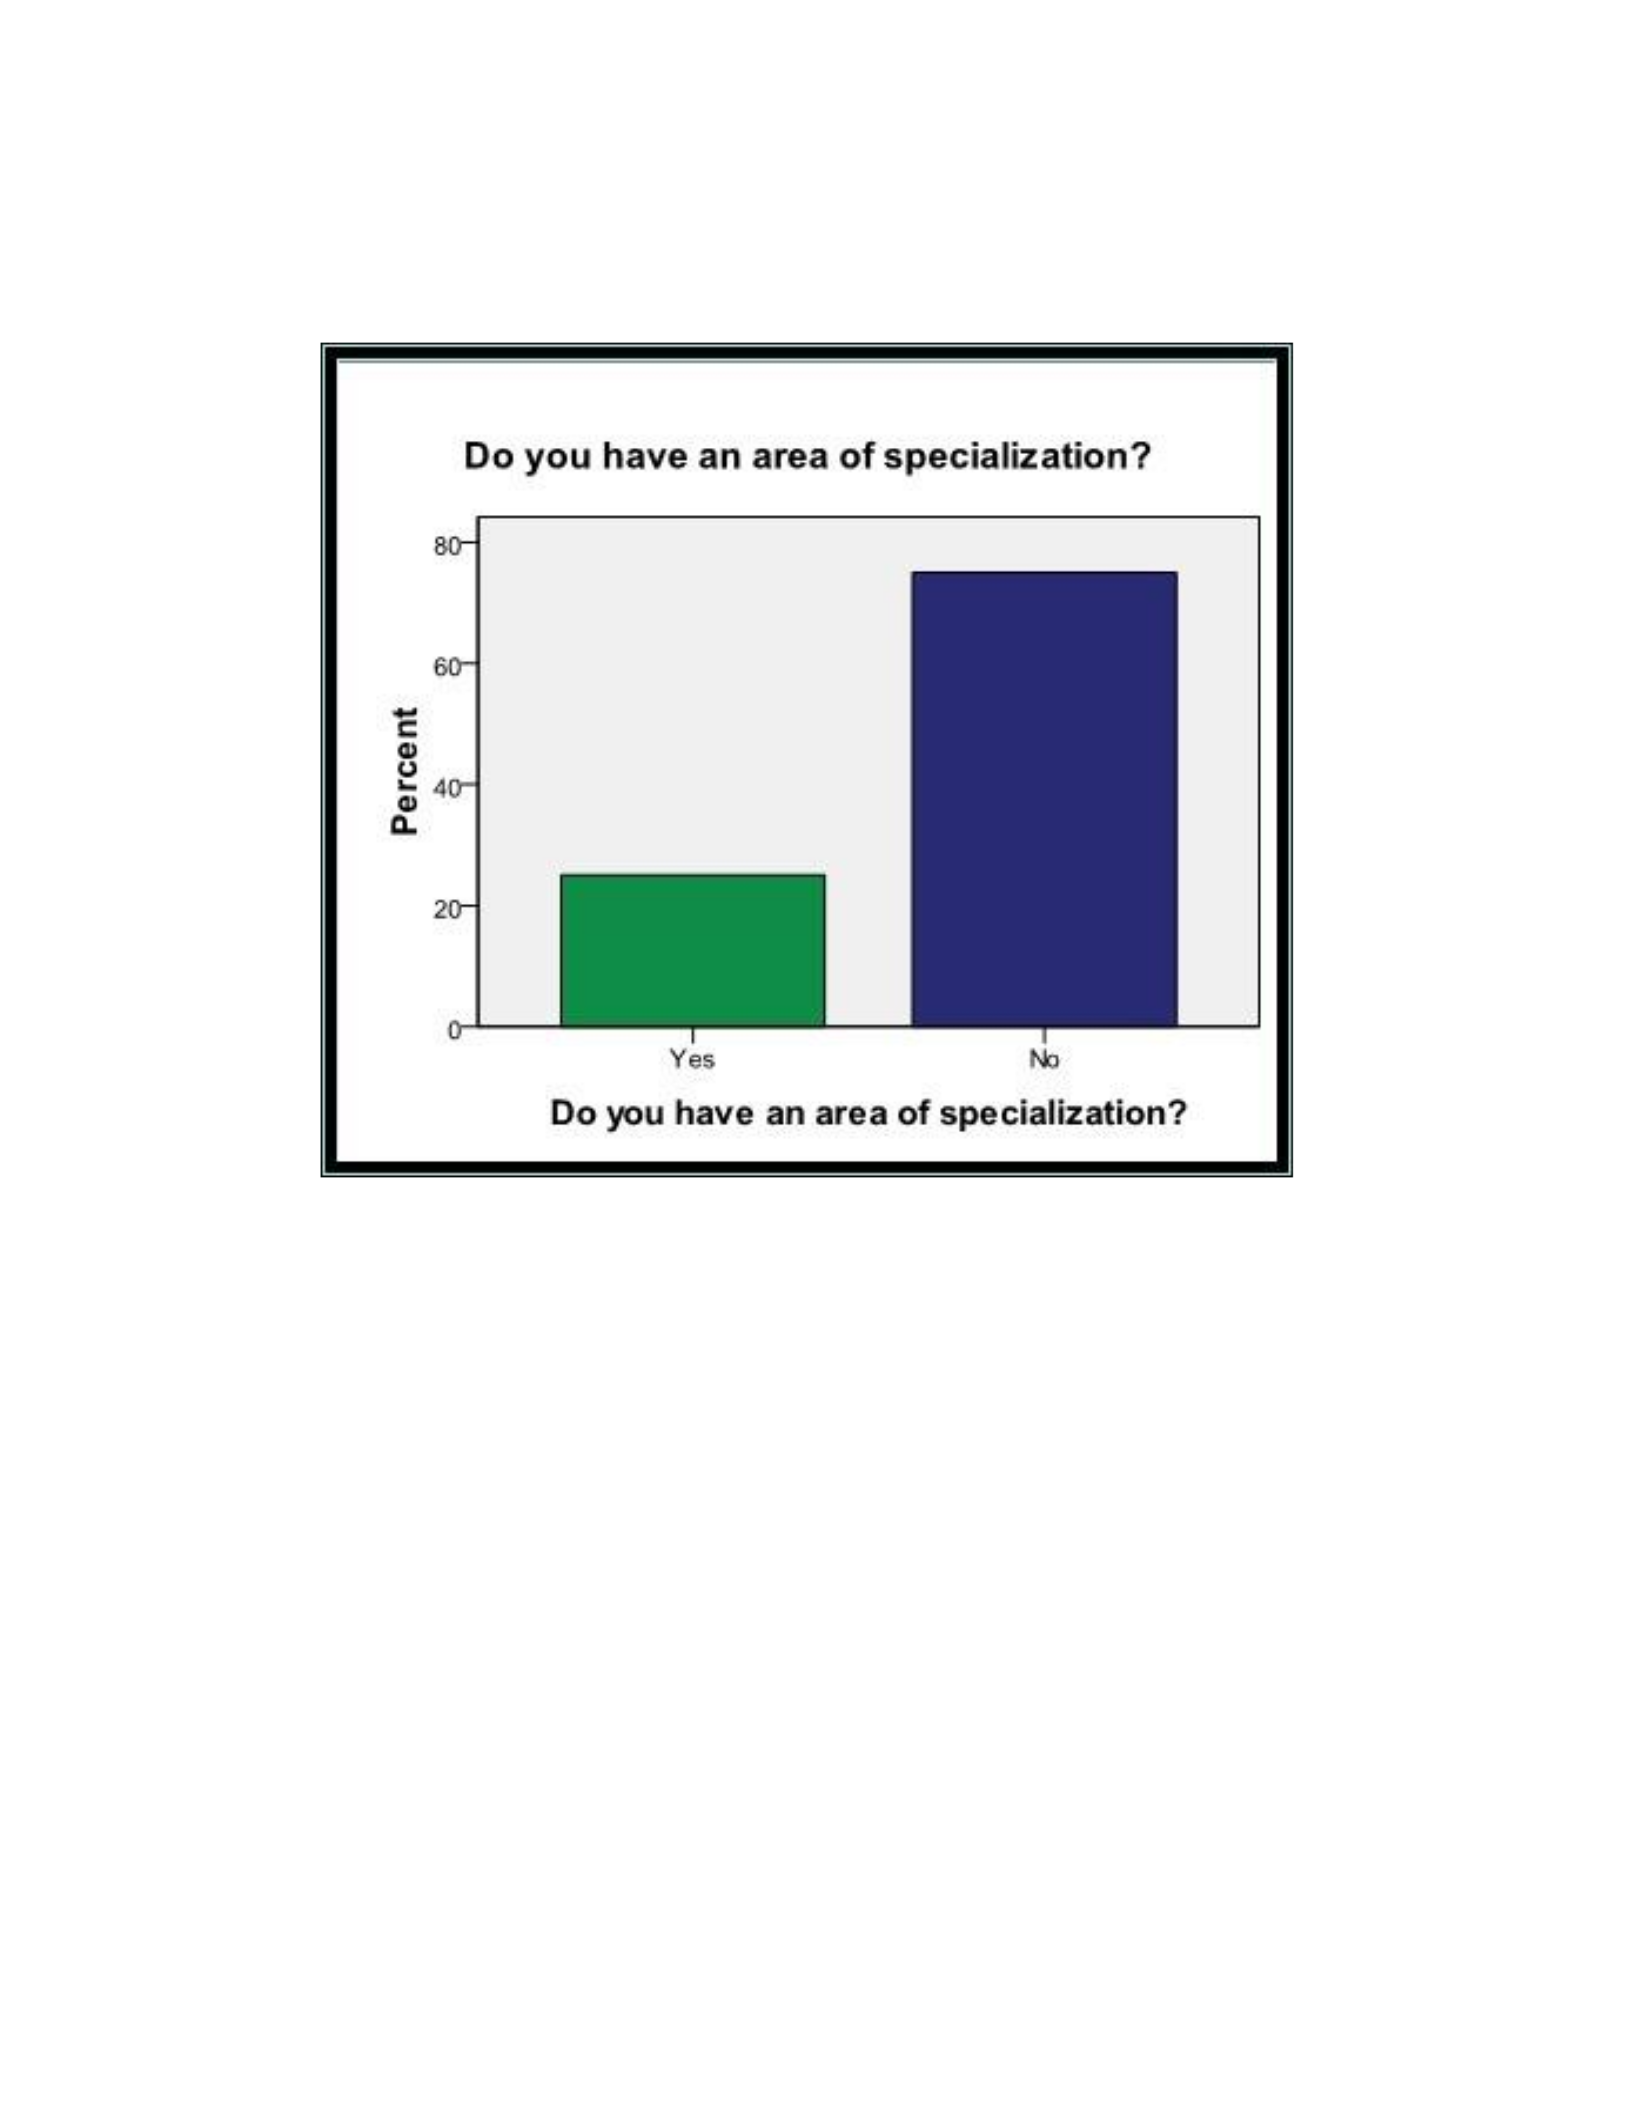
allopathic medicine, even those who were trained in Ayurveda and homeopathy. It was
explained to me that out of need and patient demand, all HCPs (excluding the bhouas)
Figure 17. Do you have an area of specialization?
identified as bhouas, and 5 percent (n = 1) indicated “Other” (Figure 18). Interestingly,
all HCPs, except the bhouas and the traditional birth attendant, told me that they practice
allopathic medicine, even those who were trained in Ayurveda and homeopathy. It was
explained to me that out of need and patient demand, all HCPs (excluding the bhouas)
practice allopathy to a greater or lesser degree. This could include the prescribing of
analgesics, antibiotics, or anti-malarials such as chloroquine, the drug of choice for
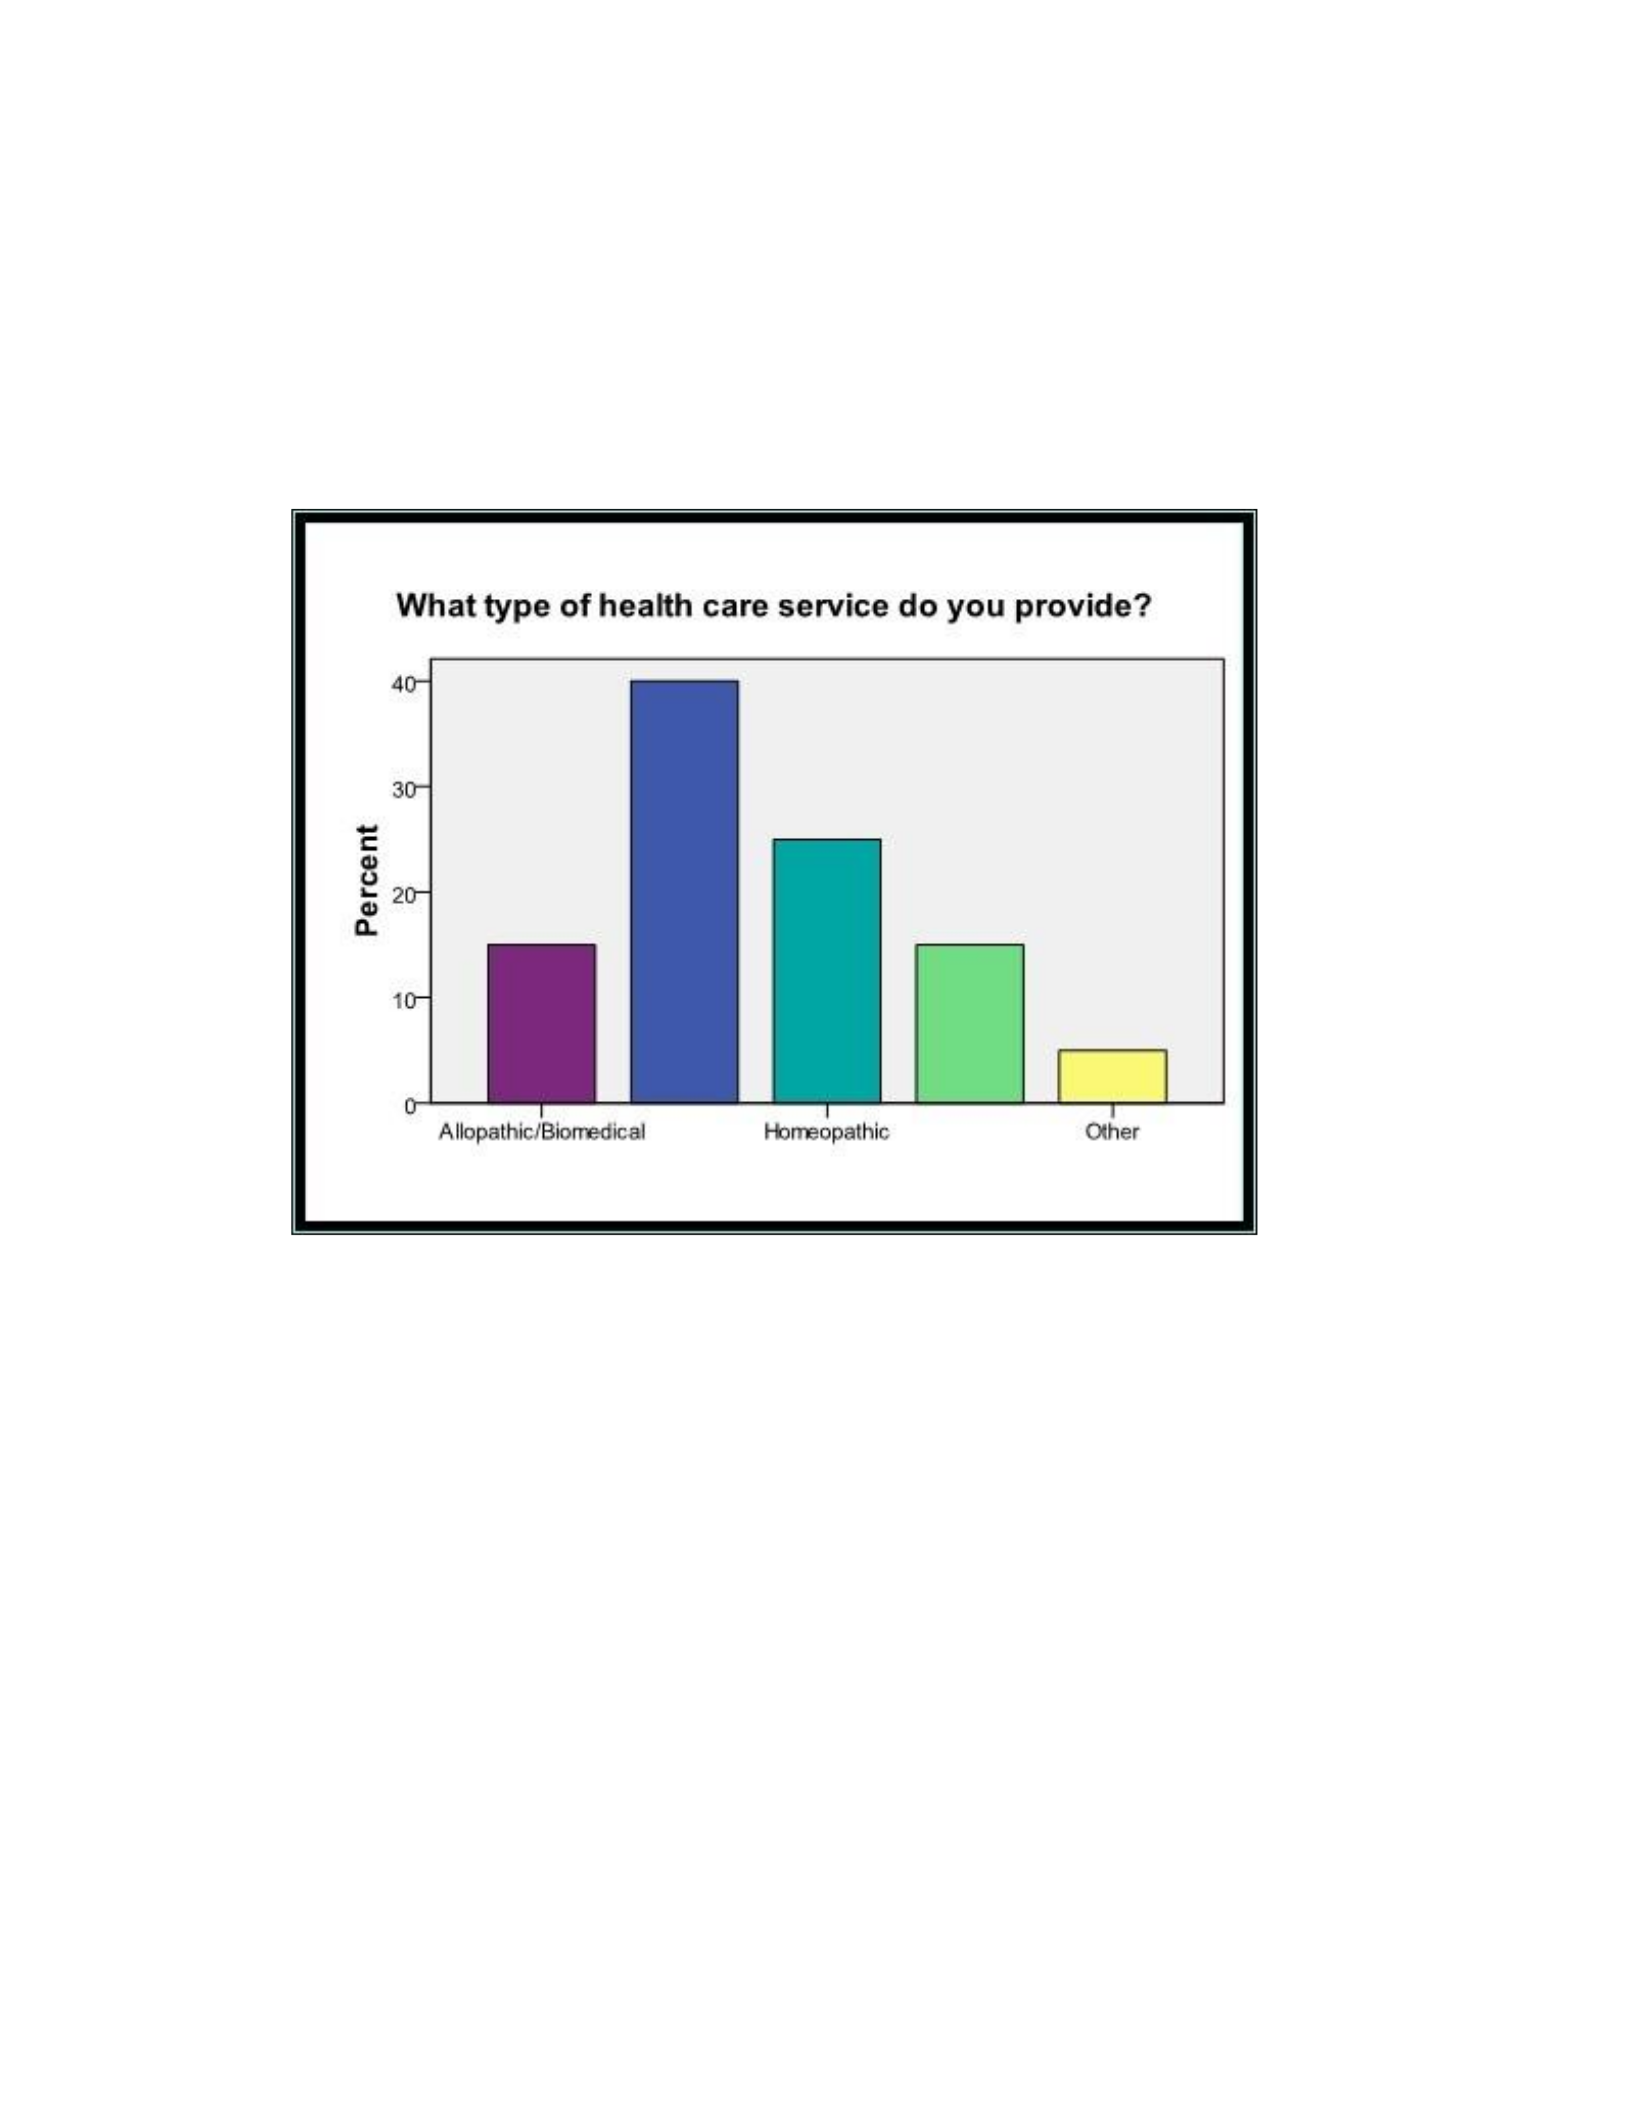
malaria in this region, taking x-rays, suturing, or giving inoculations to children. None of
the Ayurvedic or homeopathic HCPs claimed to deliver babies, though one of the bhouas
said delivering babies was one of his duties. Delivering babies was the only health care
service provided by the traditional birth attendant.
Figure 18. What type of health care service do you provide?
All HCPS were asked about their health care-related training and education, where
they went to school. Bhouas were asked how they came to be a bhoua—specifically what
prompted them to enter the realm of healing. Being a bhoua is a male vocation. One is
called or chosen by the divine to take up the work. One bhoua stated that no one taught
him to be a bhoua, that a goddess had come to him in a dream many years ago and she

gave him energy to be a bhoua. He claimed that he had supernatural powers, and thus he
was able to heal those in need. The two other bhouas were a father-in-law and his son-
inlaw. The father-in-law told me had trained the son-in-law in techniques of healing,
including the use of medicinal plants as well as which mantras to chant while treating
illnesses. Both bhouas claimed to have been called by the divine to become bhouas.
The length of time that each HCP had been practicing varied, with the majority,
55 percent, having over 10 years’ experience practicing in their respective disciplines.
Twenty-five percent of respondents (n = 5) indicated that they had been practicing between
one and three years; 15 percent (n = 3) stated they has been practicing between 4-6 years;
5% (n = 1) had been practicing 7-9 years; and 55 percent (n = 11) had been practicing over
10 years. One bhoua claimed to have been practicing for 45 years, another for 25 years.
The GMDC medical assistant had been practicing over 35 years (Figure 19).
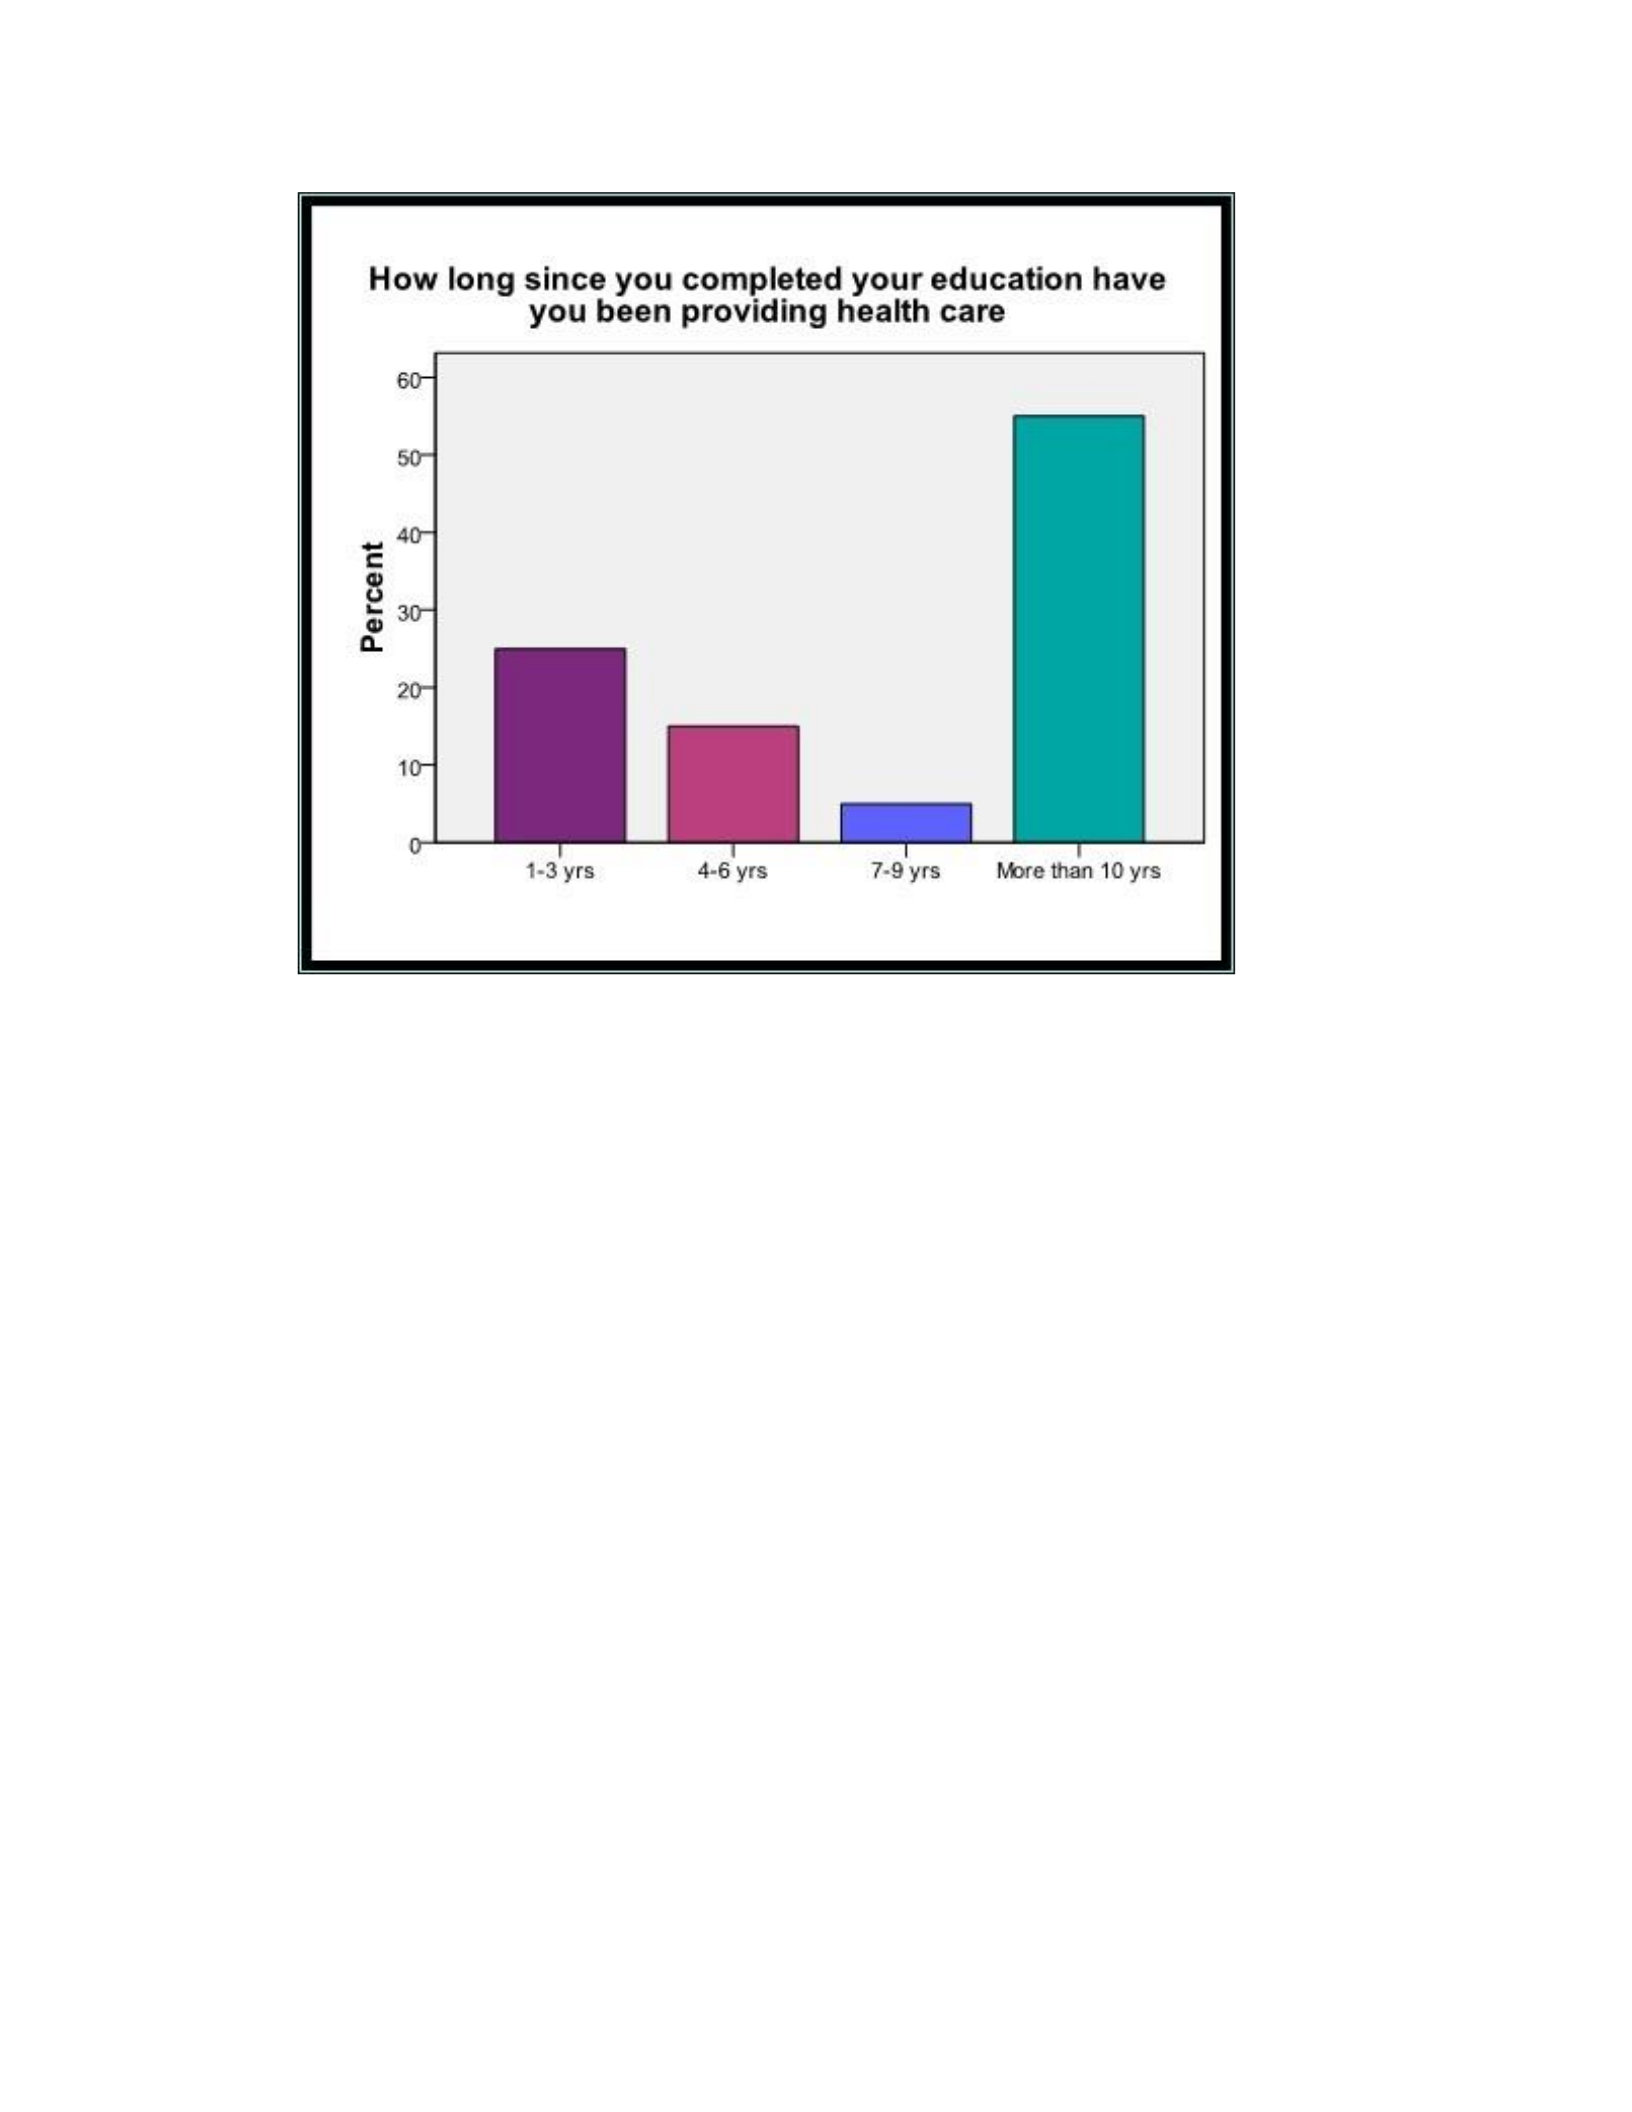
Figure 19. Length of time practicing as an HCP.
My interest was in approximately how many Rathwa from Kadipani each of these
HCPs treated per day. A closed-ended question, “Approximately how many Rathwa from
Kadipani do you treat per day?” (Figure 20) was posed with the following response
choices provided: (1) None; (2) 1-3 per day; (3) 4-6 per day; (4) 7-10 per day; (5) More
than 10 per day; (6) Other. Fifty percent (n = 10) replied “1-3 per day”; 20 percent (n = 4)
replied “4-6 per day”; 10 percent (n = 2) responded “7-10 per day”; 10 percent (n = 2)
responded “More than 10 per day”; and 10 percent (n = 1) responded “Other.”
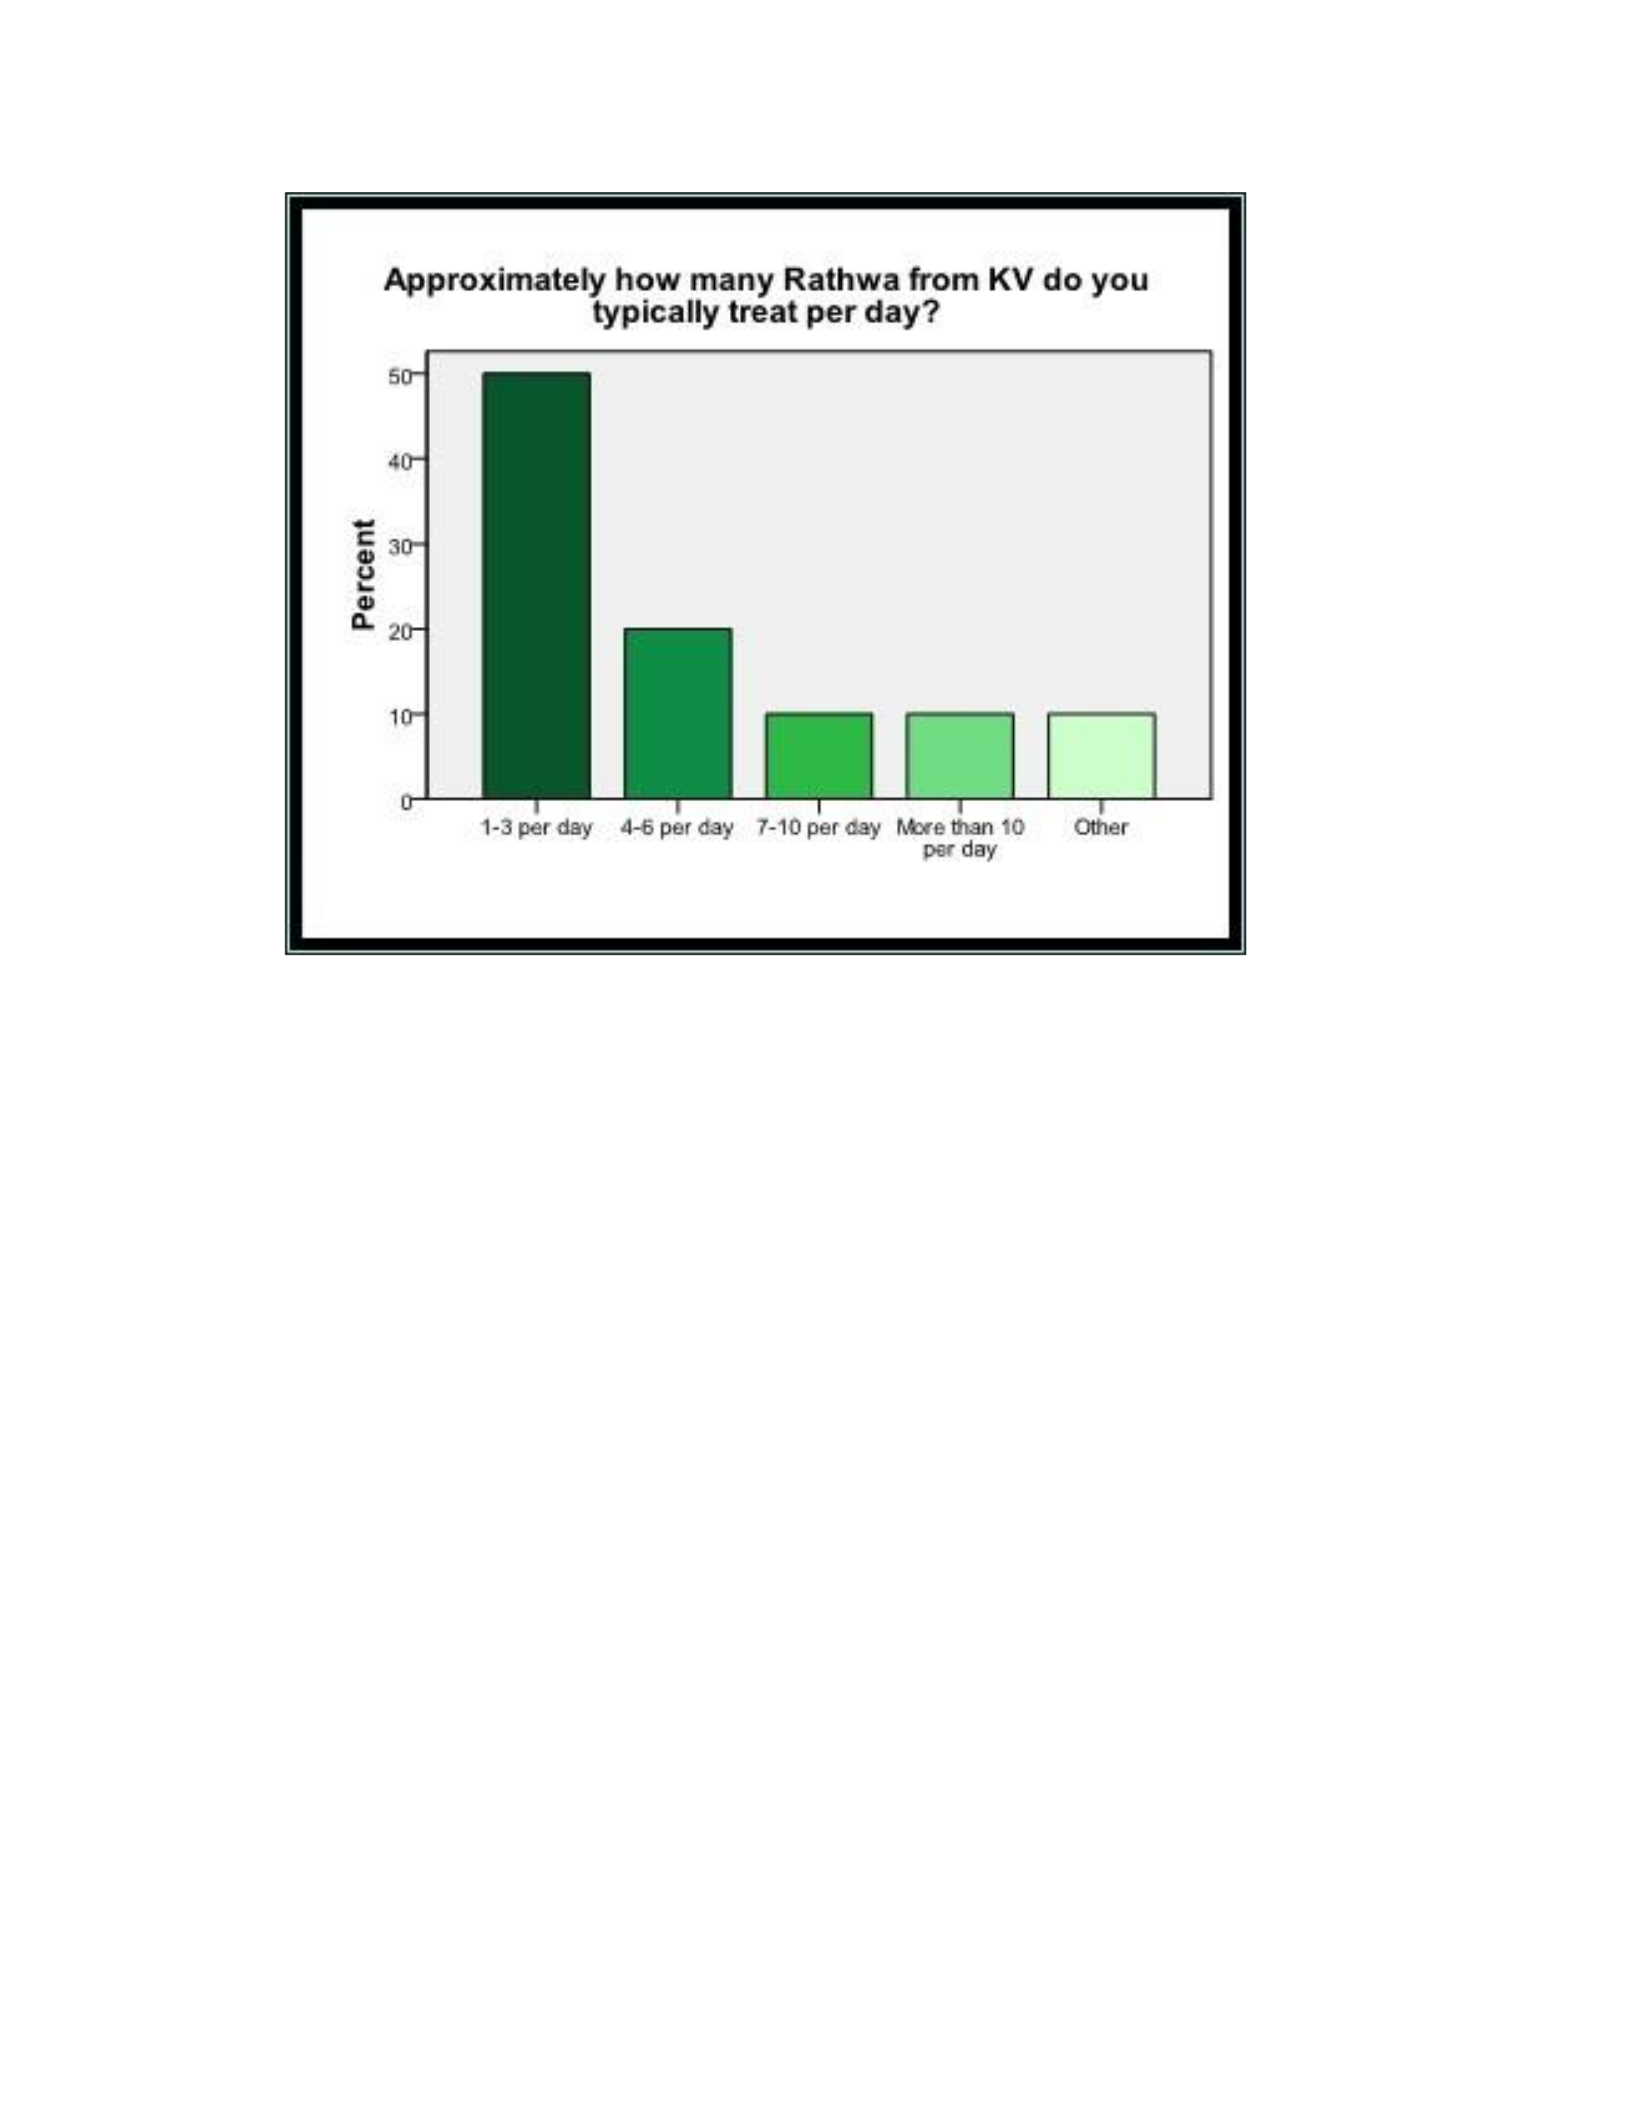
Figure 20. Approximately how many Rathwa from Kadipani do you typically treat
per day?
Since the incidence of malaria among the Rathwa was an interest in my research,
HCPs were asked “How frequently do you treat Rathwa for malaria?” (Figure 21), with
five forced-response choices. Twenty percent (n = 4) of respondents indicated that they
never treat Rathwa for malaria; 35 percent (n = 7) stated that they treat Rathwa for malaria
1-3 times per week; 5 percent (n = 1) indicated treating Rathwa for malaria 4-6 times per
week; 5 percent (n = 1) treat Rathwa for malaria more than 10 times per week; 10 percent
(n = 2) indicate treating Rathwa daily for malaria; and 25 percent (n = 5) stated “Other.”
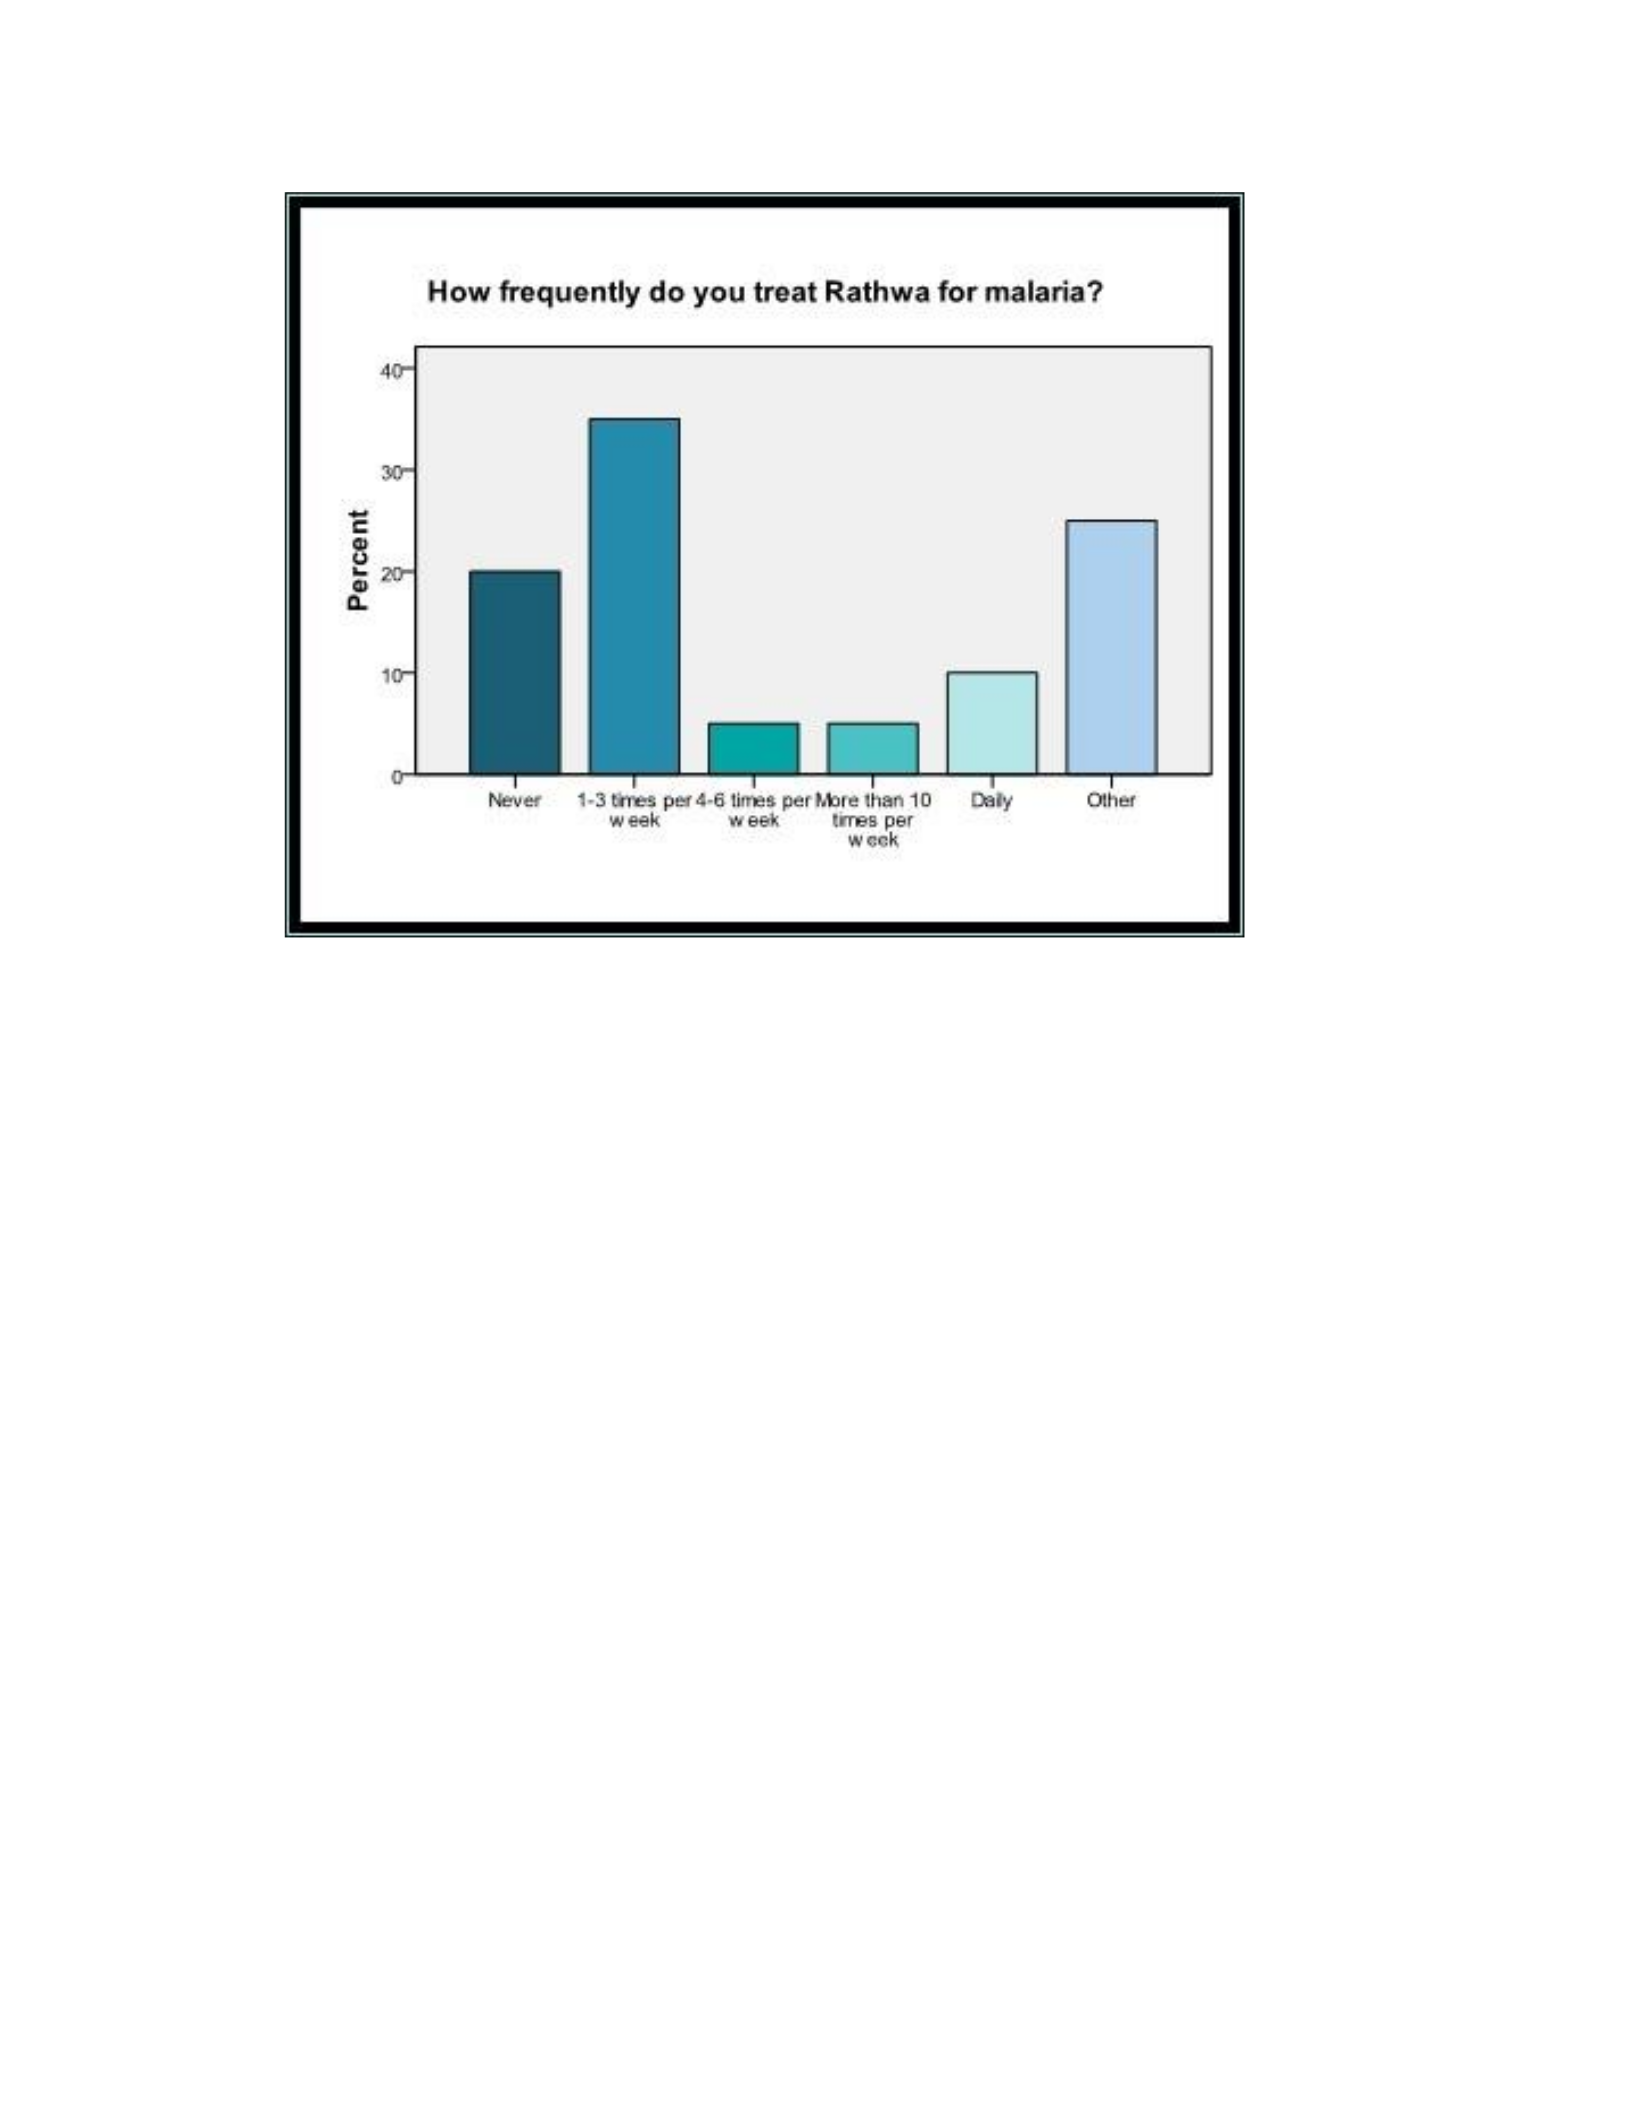
Figure 21. How frequently do you treat Rathwa for malaria?
Sickle cell disease, which may be found in populations where malaria is endemic,
and is estimated to occur in 20-30 percent of Rathwa adivasi, was also an issue key to my
research. HCPs were asked “How frequently do you treat Rathwa for symptoms related to
sickle cell anemia?” with the following forced response choices: (1) Never; (2) 1-3 times
per week; (3) 4-6 times per week; (4) 7-10 times per week; (5) More than 10 times per
week; (6) Daily and (7) Other. Twenty-five percent (n = 5) stated that they never treat
Rathwa for symptoms of sickle cell anemia; 30 percent (n = 6) indicated that they treat
Rathwa for sickle cell anemia 1-3 times per week; 15 percent (n = 3) indicated 4-6 times
per week; 10 percent (n = 2) indicated more than 10 times per week; 5 percent (n = 1)
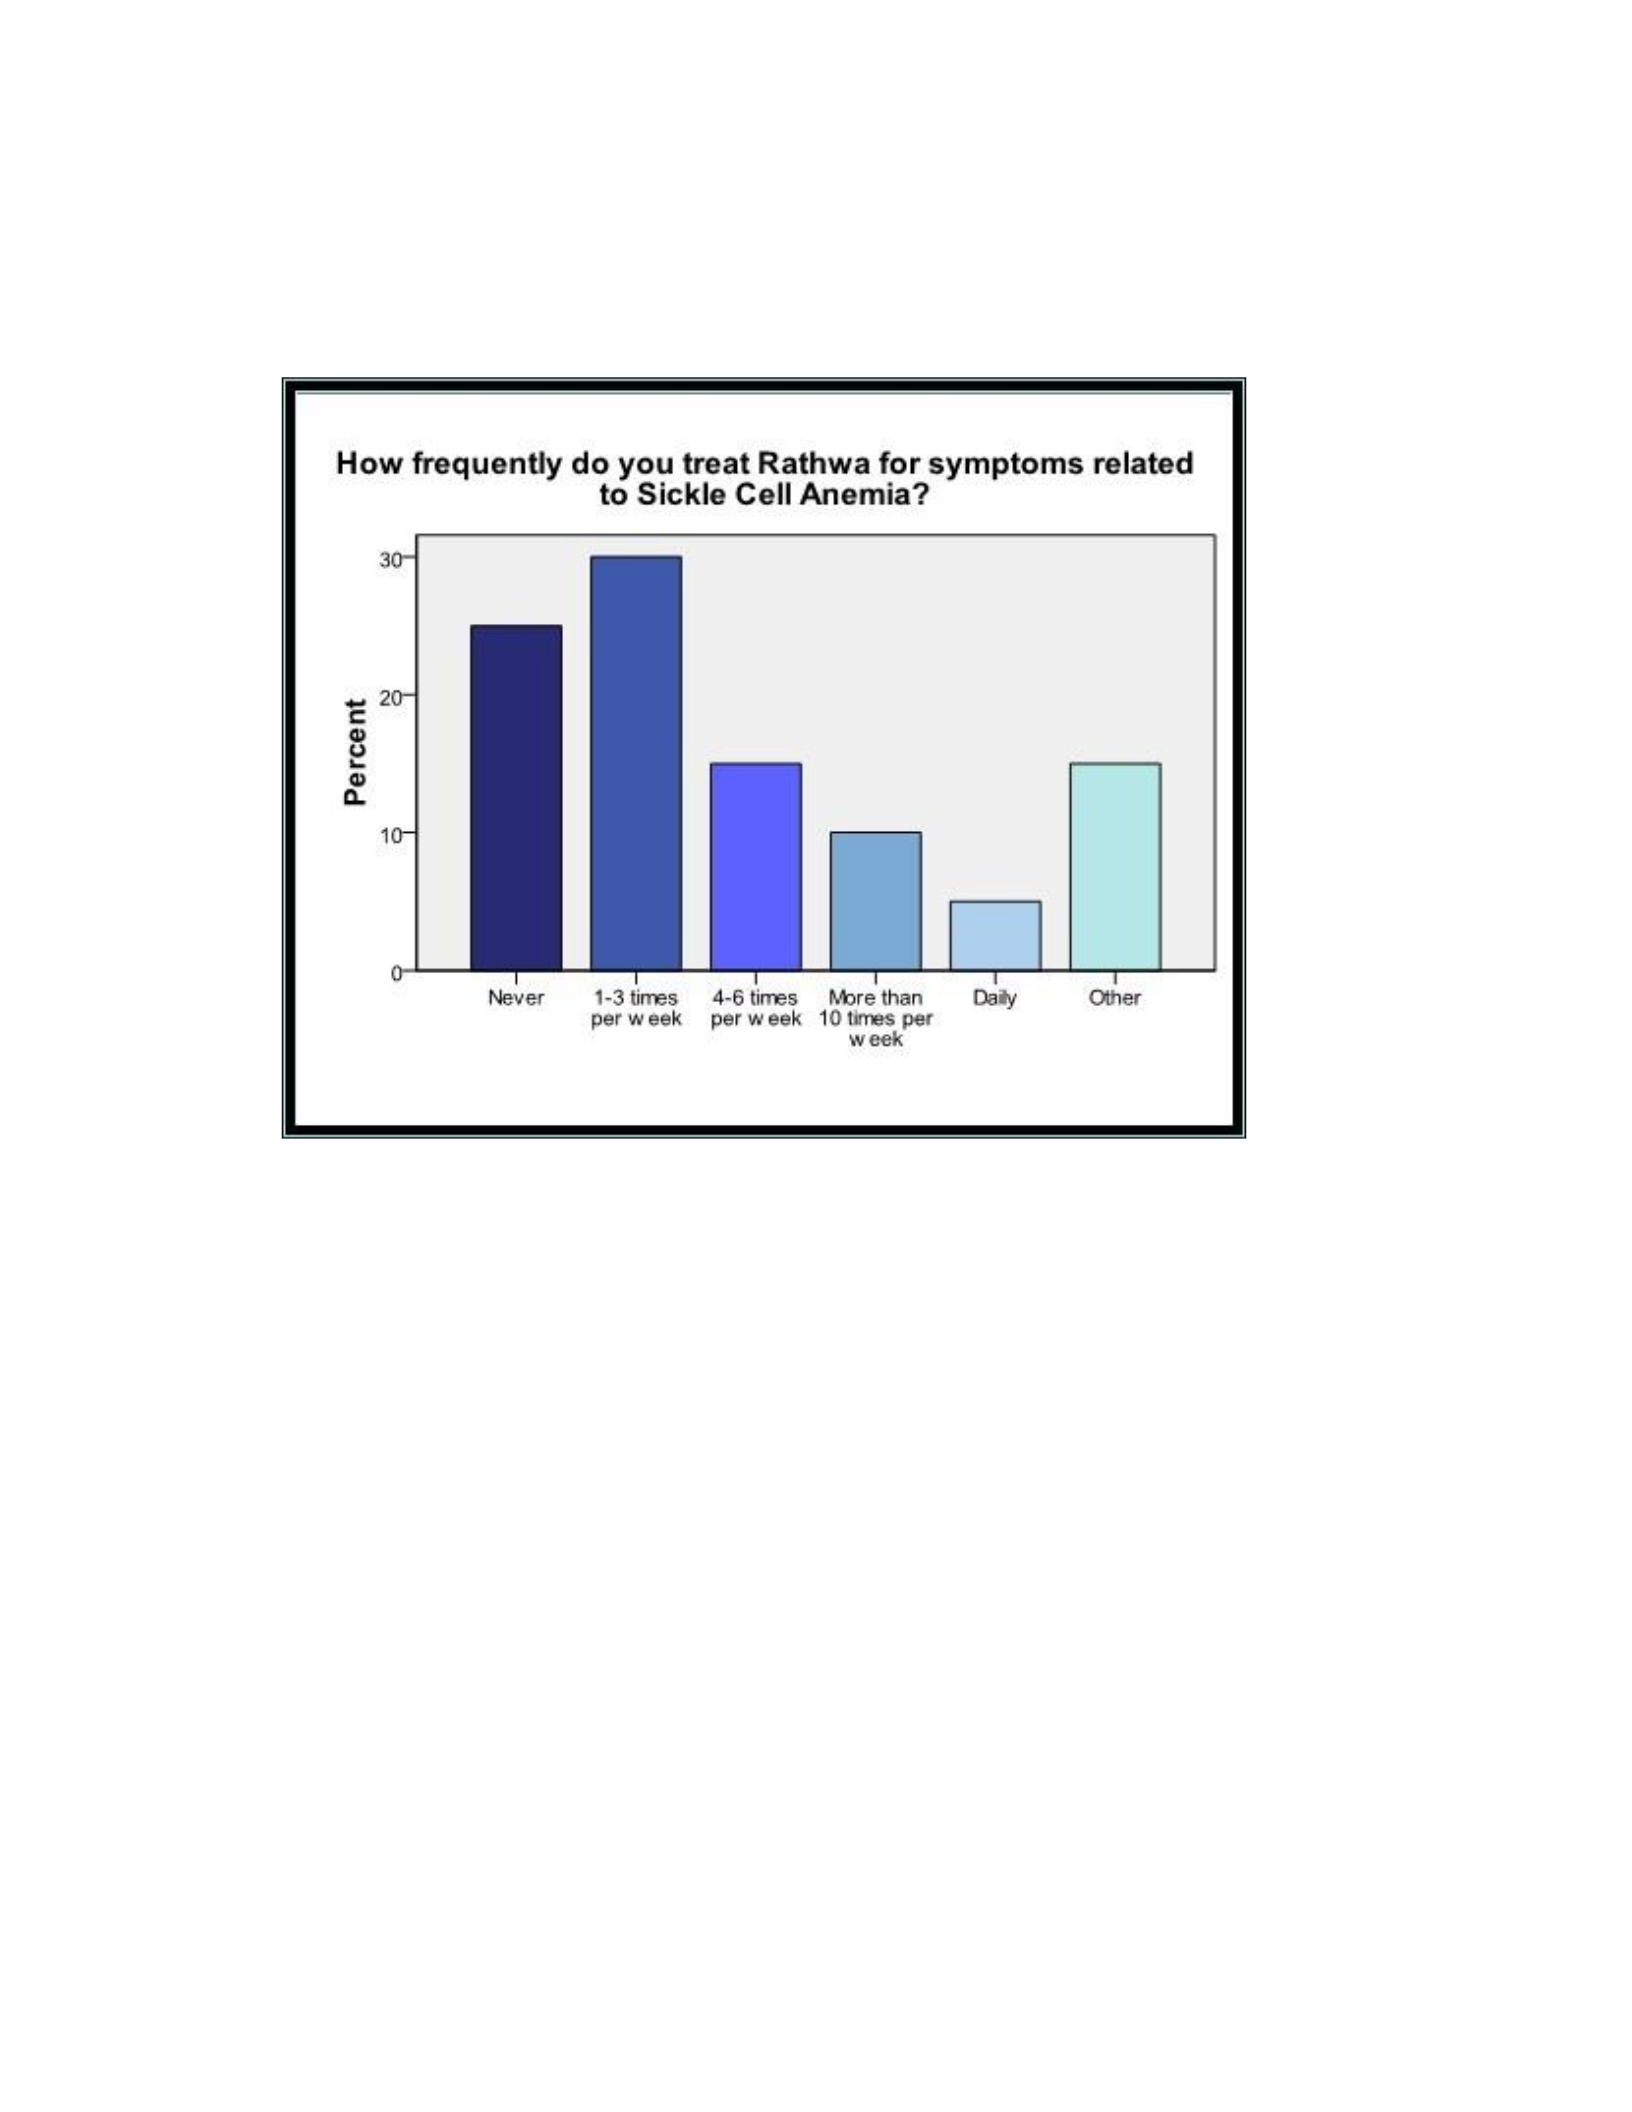
indicted treating Rathwa for sickle cell anemia daily, and 15 percent (n = 3) indicated Other
(Figure 22).
Figure 22. How frequently do you treat Rathwa for symptoms related to
sickle cell anemia?
When asked if they collaborate with other HCPs when treating Rathwa, 55 percent
(n = 11) stated “Yes” and 45 percent (n = 9) stated “No.” All HCP interviewees (n = 20)
responded “Yes” when asked, “Do your Rathwa patients use the services of other health
care practitioners, including those of a bhoua, while they are receiving treatment from
you?” Ninety-five percent (n = 19) of interviewees stated that Rathwa patients do not ask
what type of HCP they are. Fifty-five percent (n = 11) of HCPs do not tell their patients
what type of health care services they provide. I discovered while interviewing Rathwa

that they use the term “doctor” for anyone, except bhouas, who provides health care-related
services. People rarely knew what type of HCP (e.g., allopathic, Ayurvedic, or
homeopathic) they were visiting. However, they did distinguish between those in the
public sector, where they could receive free services, and those in the private sector, where
patients had to pay a fee. Interestingly, a few Rathwa respondents would only see a bhoua
for health care needs, with one female respondent stating that she did not trust doctors. Six
percent (n = 7) of respondents never went to the bhoua regardless of the illness, instead
going to either the public or private clinics, depending on the type of illness, the cost, and
the recommendations of others who had seen that same practitioner and had received
favorable service. One woman told me that she delivered a baby via cesarean section in the
public hospital, had difficulties with the birthing process, needed a blood transfusion, and
was subsequently diagnosed with sickle cell disease. Due to the trauma of this experience,
and lingering pain after the procedure, this woman had little faith or trust in biomedical
doctors and avoided using their services whenever possible.
When asked “How would you rate the general health status of the Rathwa, with
forced response choices of: (1) Excellent; (2) Good; (3) Fair; (4) Bad; and (5) Don’t know,
60 percent (n = 12) rated Rathwa health status as “fair”; 30 percent (n = 6) rated it “bad”;
and 10 percent (n = 2) stated they “don’t know.” One HCP said he could not assess Rathwa
overall health status as he was fairly new to the area and did not know many of the people.
It was interesting and telling that none of the HCPs rated Rathwa health status as excellent
or good. I was not necessarily surprised by this, but I was concerned to know why these
HCPs believed this.

When I asked an open response question probing each HCP as to why he or she
rated Rathwa overall health status as they did, some of the responses included: “People are
poor, they don’t have any money, and life is hard”; “Hygiene is a problem, this leads to
illness”; “People are malnourished, they are ignorant about nutrition, eating just maize,
rice, and cereals”; “Their belief systems, they believe diseases are caused by angry gods,
black magic and witch craft”; “Lack of education”; “First they go to the bhoua, the
problem gets worse, then they go to a doctor”; “Drinking alcohol”;” Poor immunity”;
“Lifestyle”; “Addiction—alcohol, smoking, chewing tobacco”; “Hard, overwork”
“Carelessness”; “Bad water, especially river water”; “Lack of proper knowledge.”
All HCPs indicated that poor hygiene, which included the lack of bathing, or
bathing with one’s clothes on, was a serious concern, as was the practice of not wearing
shoes and walking in areas where people defecate, which lead to people becoming infected
with worms. All HCPs interviewed stated that malnutrition, or the limited diet of the
Rathwa, was a strong factor in their poor health status. The Rathwa diet consists mostly
of maize, with very little protein. Unclean water for both drinking and cooking was
mentioned repeatedly by HCPs as a cause of poor health. When I surveyed Rathwa
households, I asked were they obtained water for cooking and drinking. Ninety-one
percent (n = 91) of Rathwa get their water from hand pumps, 13 percent (n = 16) from local
wells,
9 percent (n = 11) from a tap in the vicinity of their homes, and 3 percent (n = 3) from the
Narmada River. During a trip I made with my survey workers to the Narmada River, I

observed people as well as animals bathing in the river in the same area where people were
collecting water for drinking and cooking.
Lack of knowledge or formal education about the prevention or treatment of
illnesses such as malaria, diarrhea in babies and young children, respiratory infections, or
sexually-transmitted infections was cited as a concern by the HCPs. They believed that
with more education and knowledge, the Rathwa would be able to make better
healthrelated decisions. This concern included Rathwa beliefs about the causes of
illnesses. The practice of going first to the bhoua for treatment was viewed by non-bhoua
HCPs as the source of many treatable or preventable health problems. Non-bhoua HCPs
believed that this pattern of Rathwa decision-making caused new health-related problems
or exacerbated existing ones. When I asked the HCPs what they thought the Rathwa
believed caused illness and disease, the responses included: “They do not know about these
things”;” Superstition”; “Black magic”; “Angry gods” and, “Witchcraft.” During my
structured interviews with a random sample of Rathwa, their responses to the same
question of what causes sickness mirrored those of the HCPs, apart from some who did
know that mosquitoes cause malaria, and that drinking unclean water can make you sick.
Structured Interviews with Rathwa Adivasi Living in Kadipani Village
Structured interviews (n = 30) were conducted with Rathwa living in Kadipani.
Twenty-five percent of Rathwa households (n = 30) participated in structured interviews,
with 33 percent (n = 10) of interviewees being male and 67 percent (n = 20) being female
(Figure 23). Interviewees ranged in age from 21 to 65 years, with a mean of 36, median of
35 years, and mode of 45 (Figure 24). Seventy-seven percent (n = 23) of interviewees
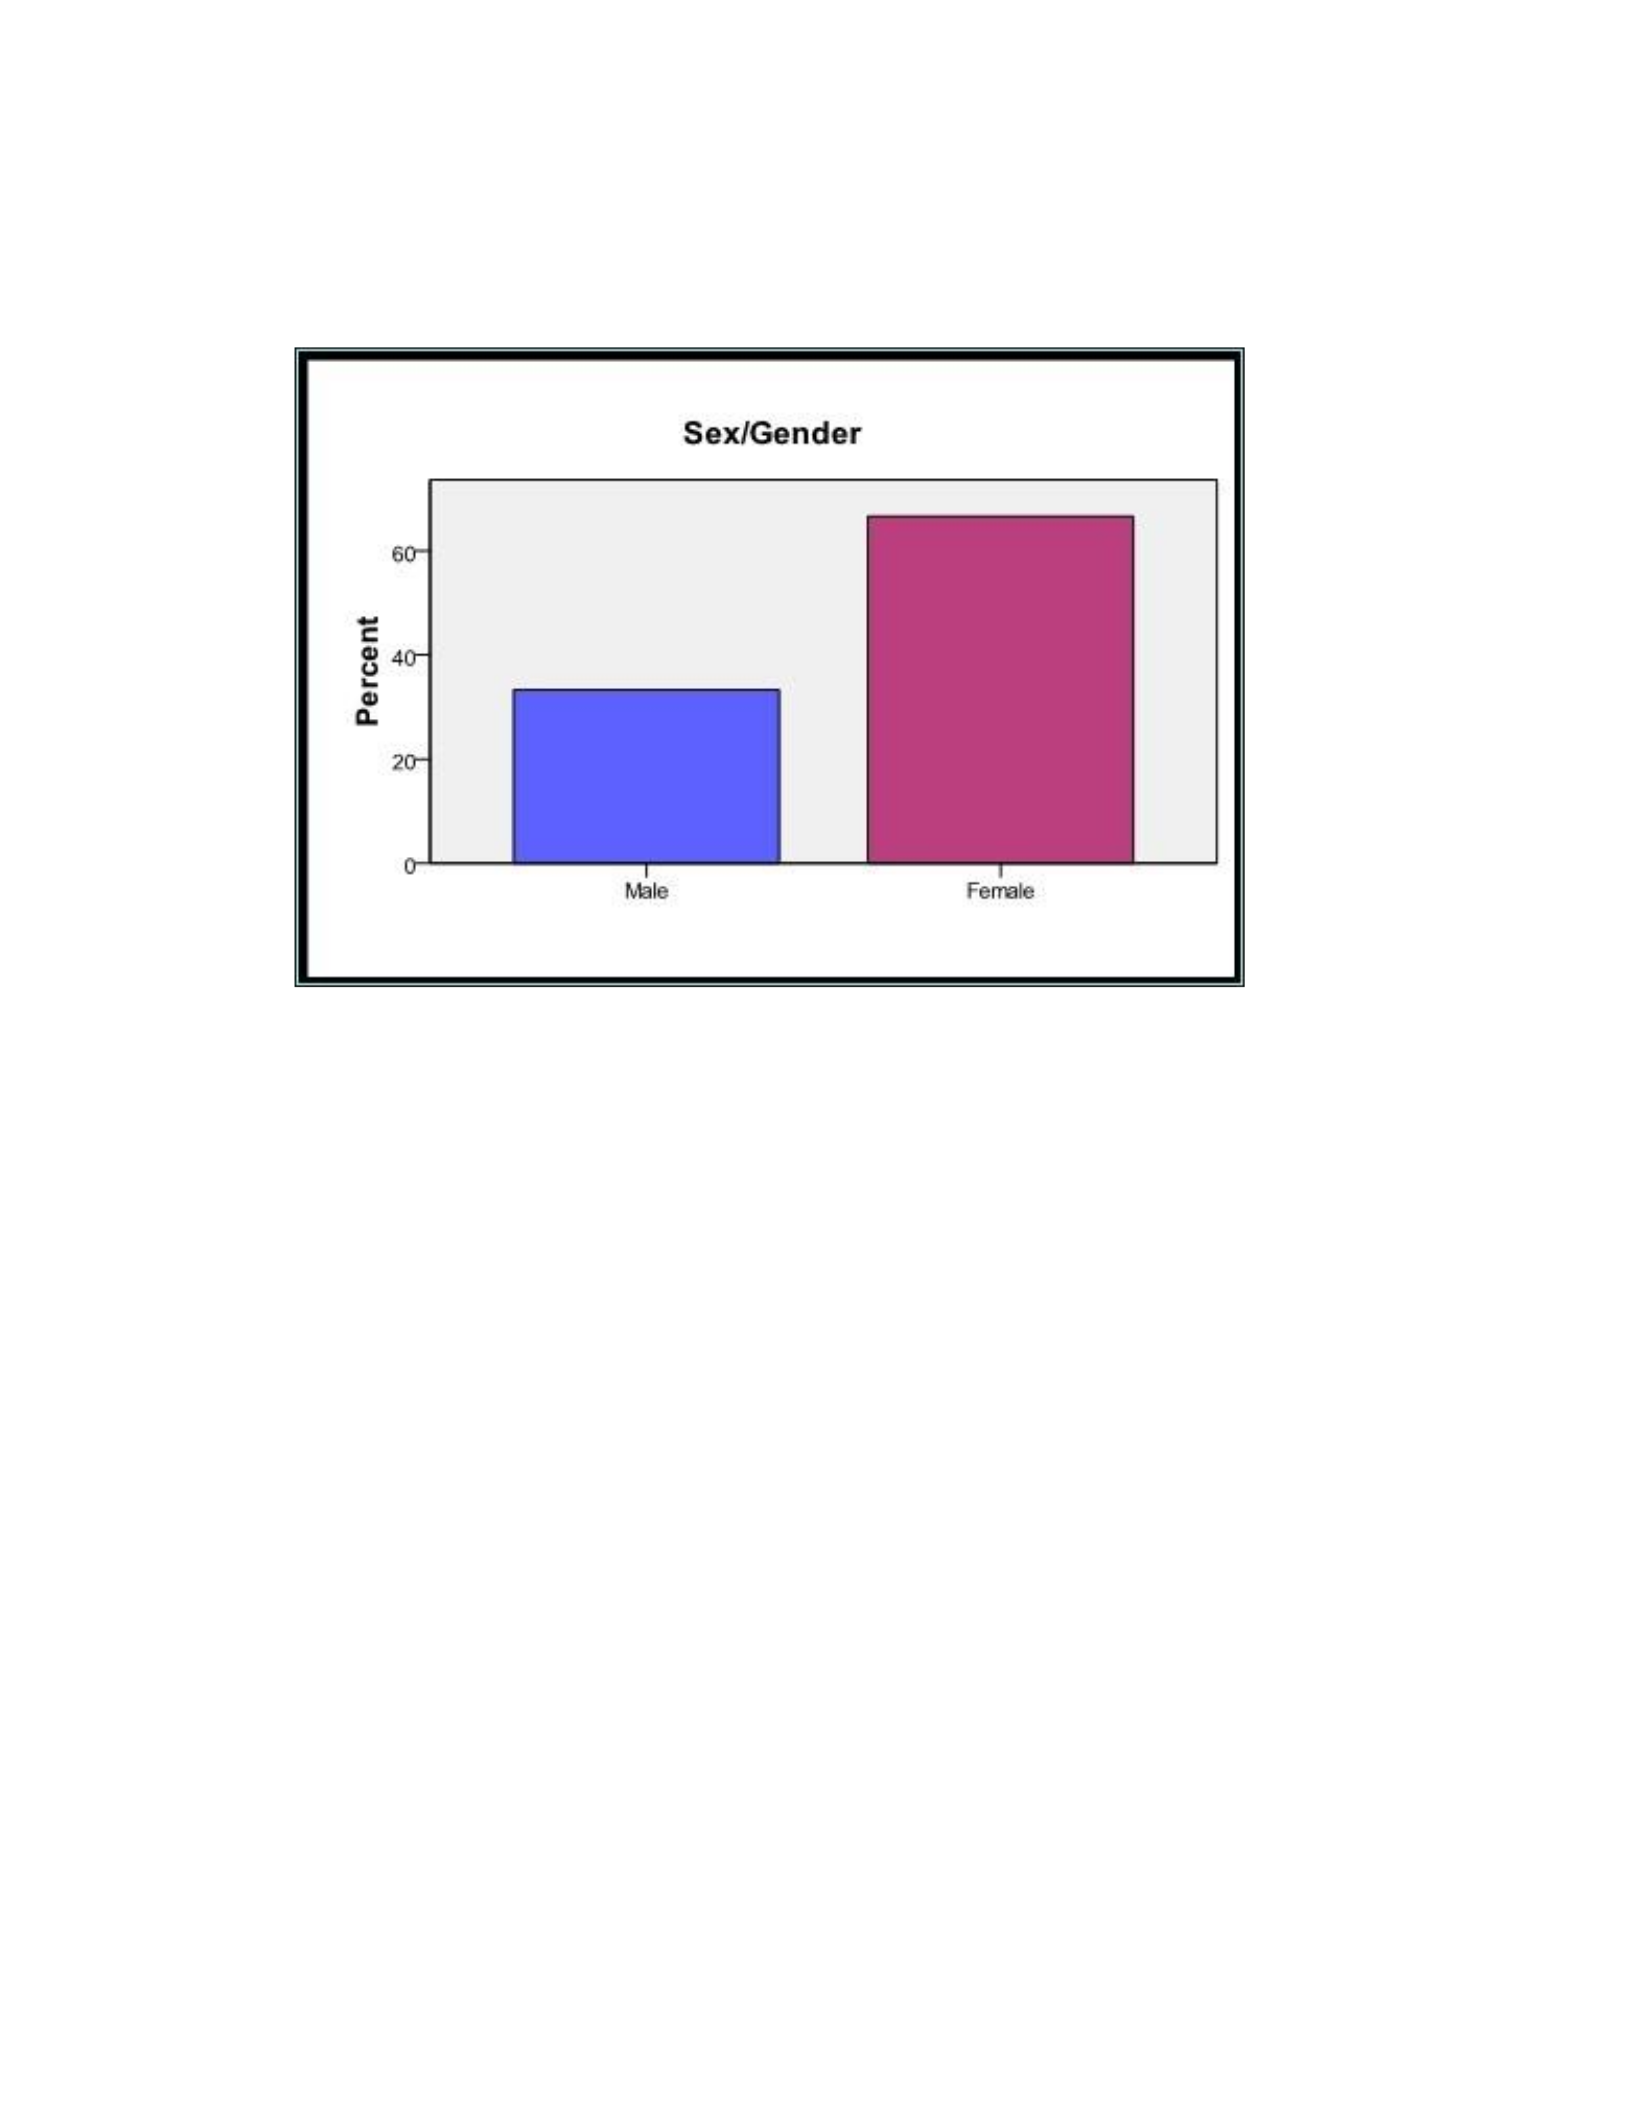
stated they worked as farmers, 13 percent (n = 4) were laborers, 7 percent (n = 2) worked
for GMDC, and 3 percent (n = 1) identified as a housewife (Figure 25).
Figure 23. Respondent sex/gender.
Responses to the closed-ended question “How good is your health” varied, with
13 percent (n = 4) replying “Excellent”, 53 percent (n = 16) “Good”, 17 percent (n = 5)
“Fair” and 17 percent (n = 5) “Poor” (Figure 26).
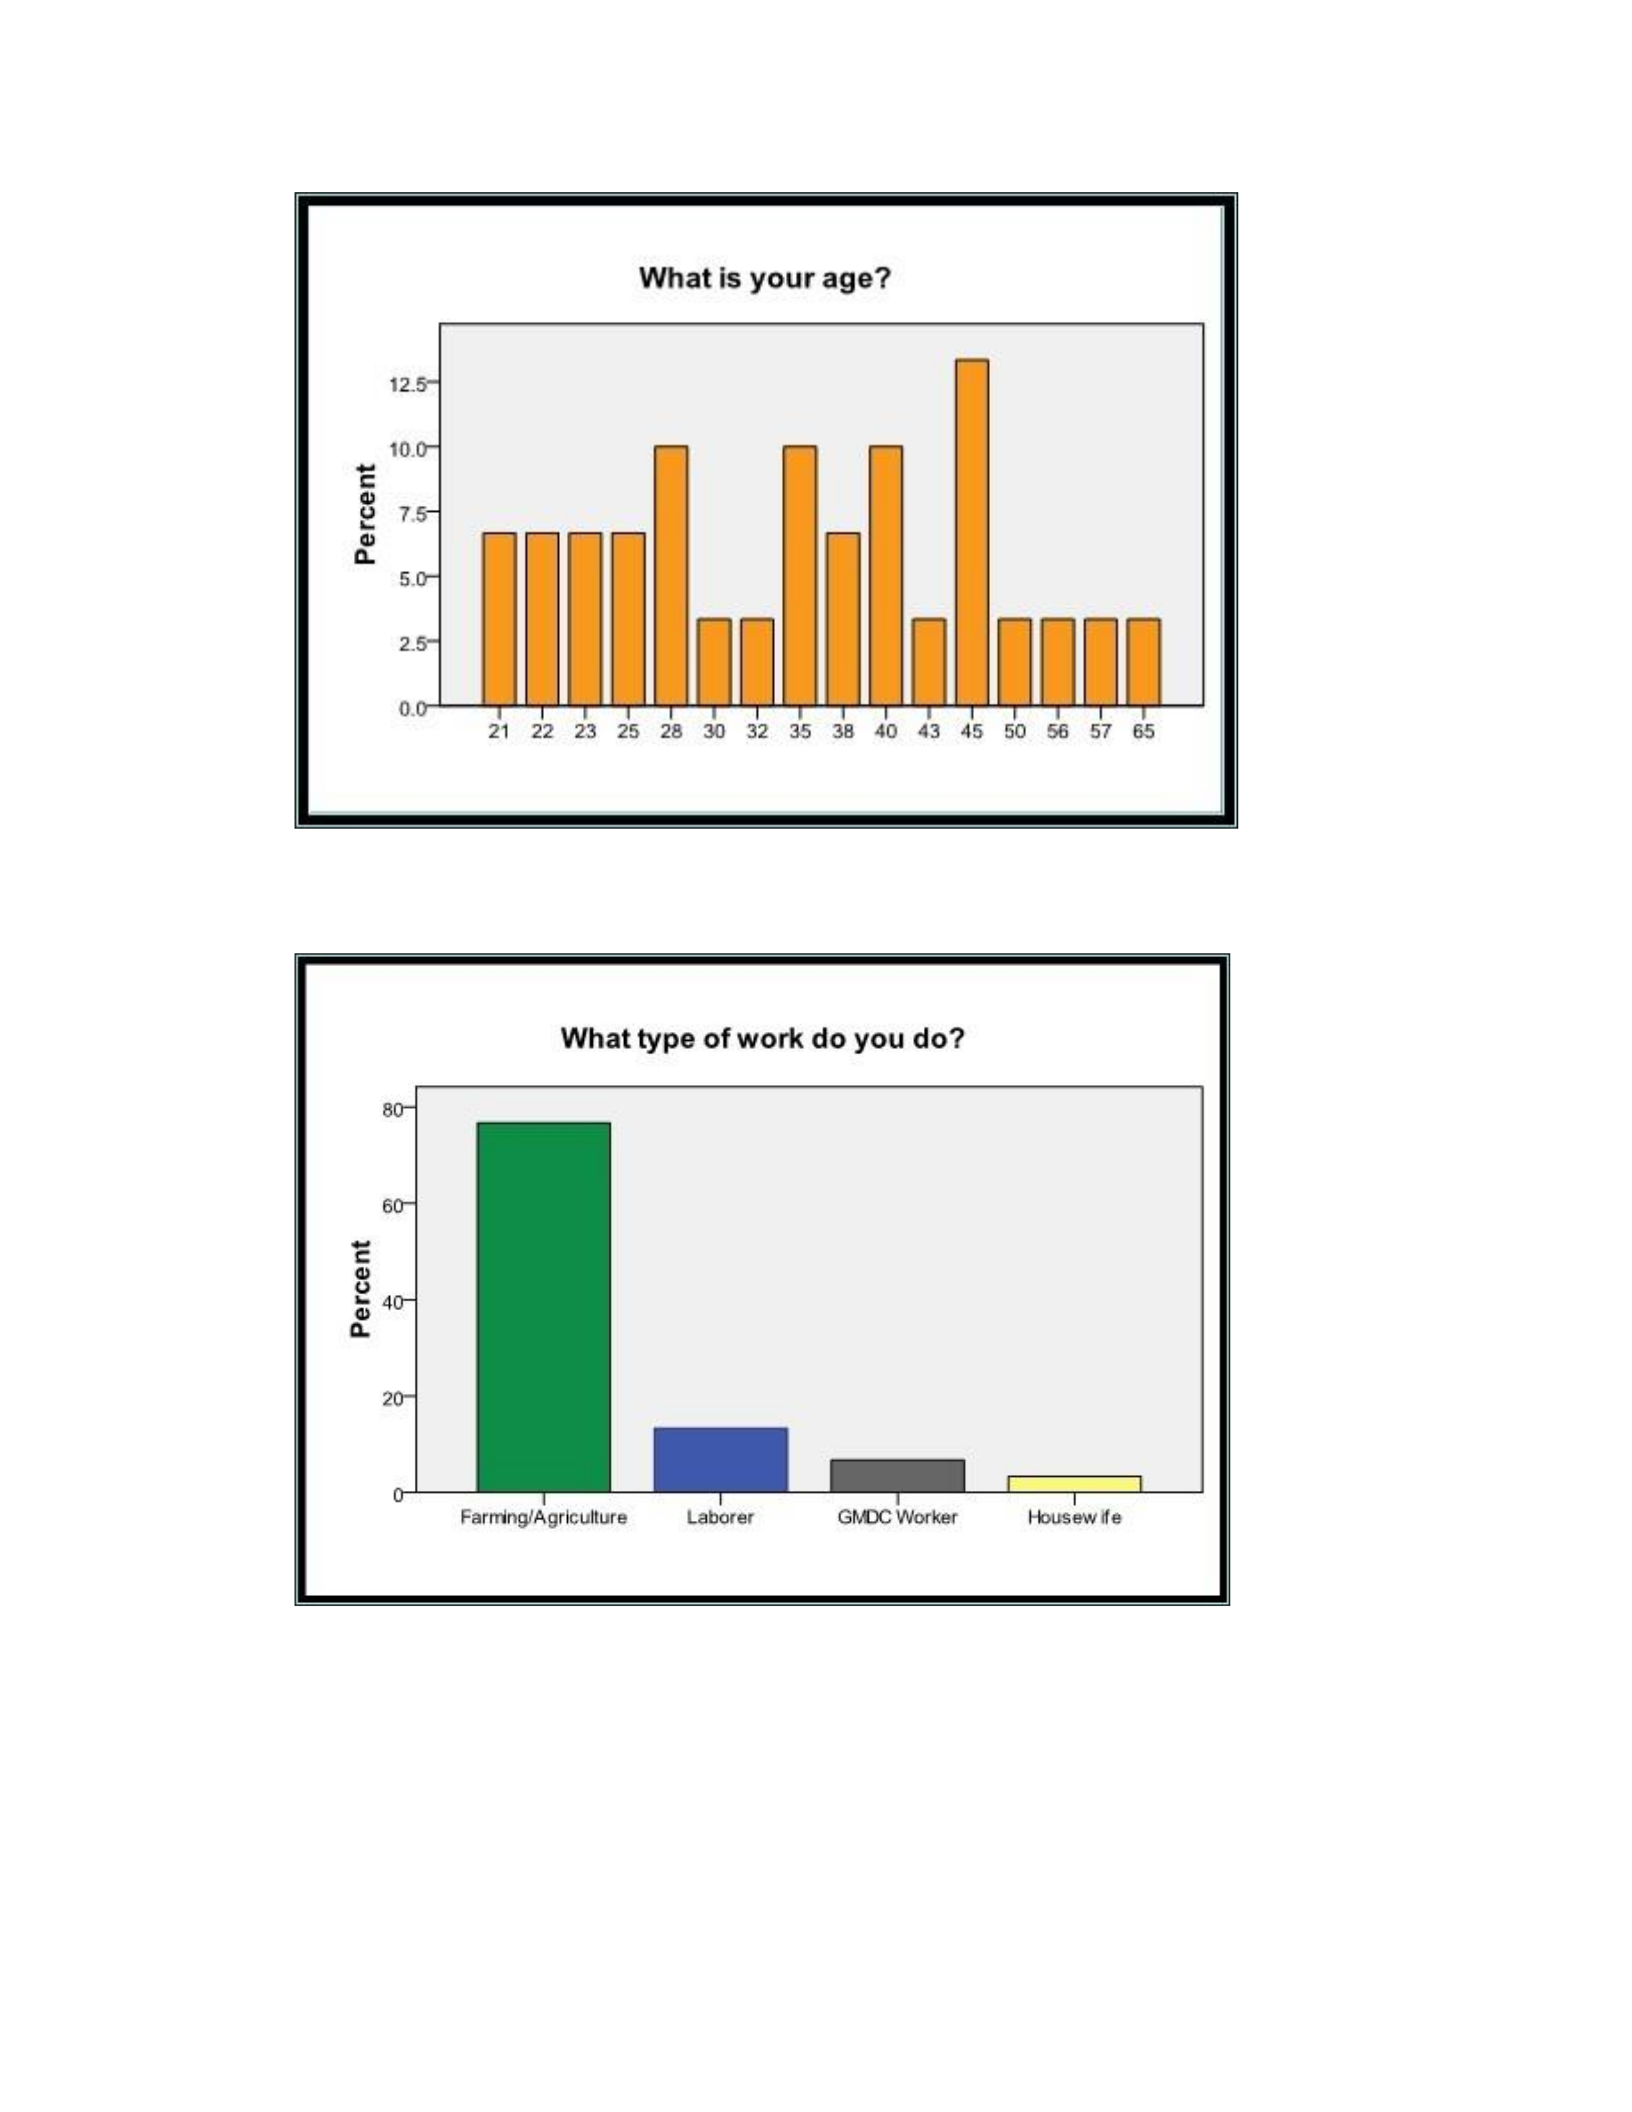
Figure 24. Respondent age.
Figure 25. Respondent employment.
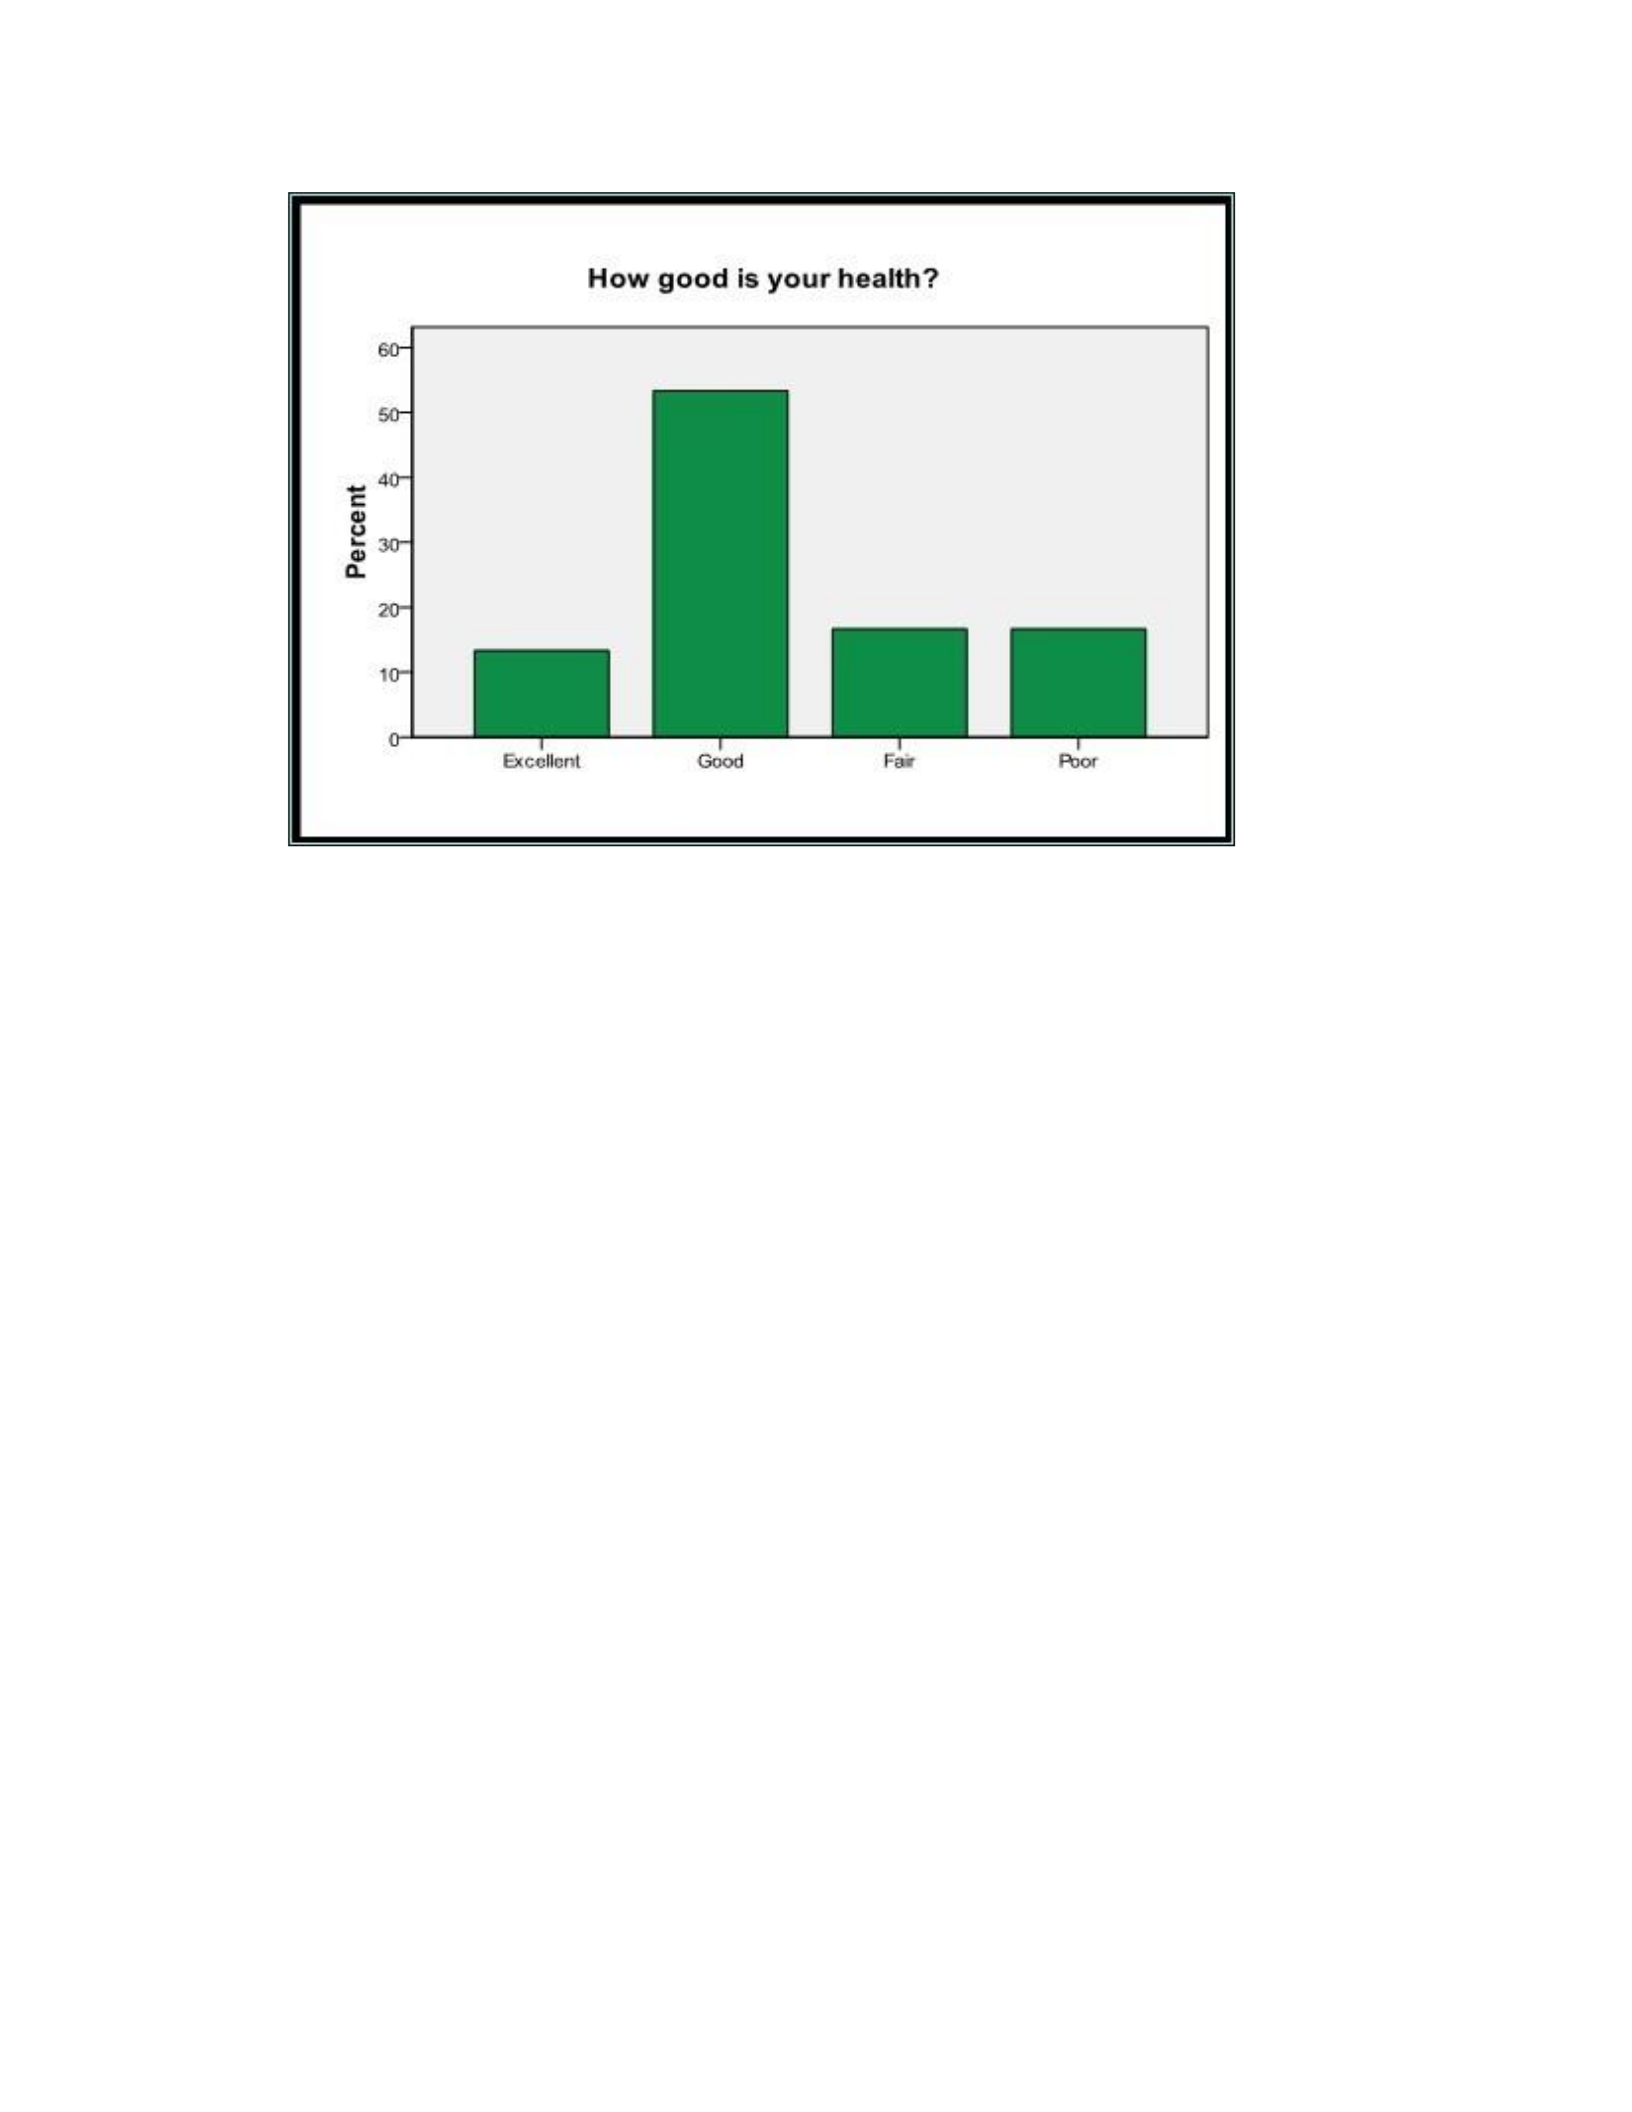
Figure 26. How good is your health?
Interviewees were also asked how frequently they visit three types of HCP: (1) a
bhoua; (2) a doctor at a government clinic or hospital; and (3) a doctor at a private clinic.
When asked “How often do you go to a bhoua when you or a person in your family is
sick?” 3 percent (n = 1) of respondents replied “Never”, 37 percent (n = 11) “Sometimes,”
30 percent (n = 9) “Almost always” and 30 percent (n = 9) replied “Always” (Figure 27).
Interviewees were also asked how often they see a doctor at a government clinic (Figure
28) and how often they see a doctor at a private clinic (Figure 29). Prior to asking the
question and providing the forced-response answer choices, I explained what each answer
meant. Ten percent (n = 3) of interviewees replied that they “never” see a doctor at the
government clinic. Twenty-three percent (n = 7) stated “sometimes,” 37 percent (n = 11)
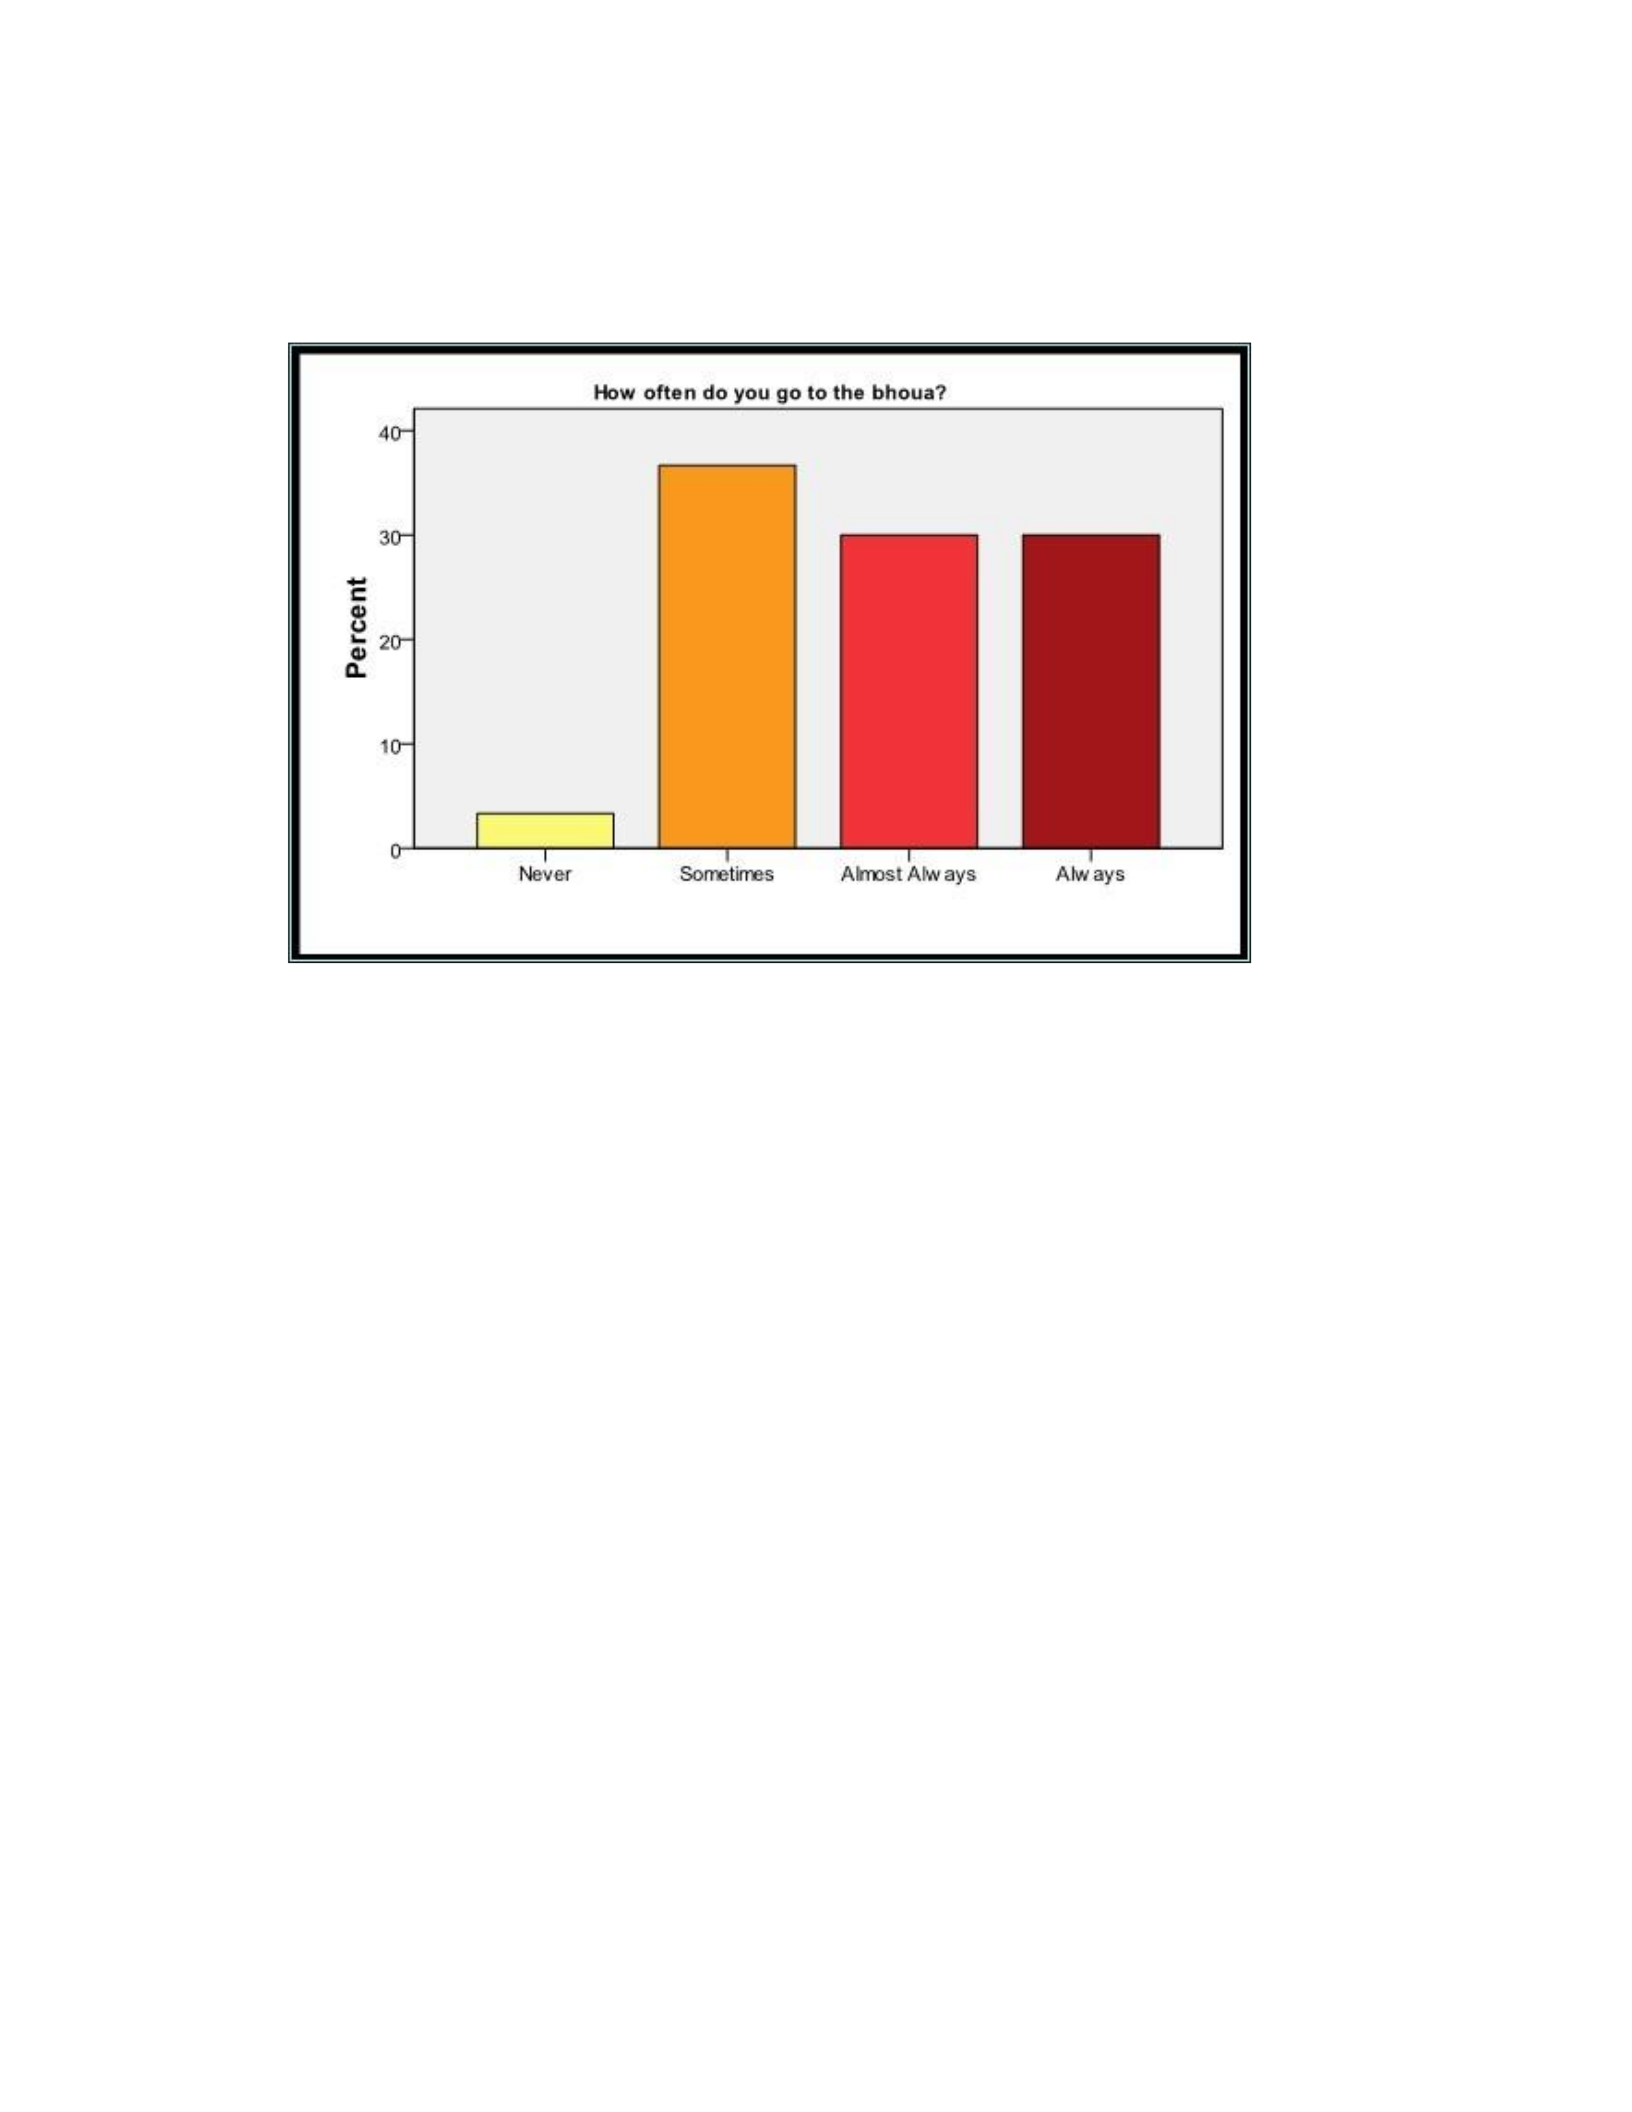
stated “almost always,” and 30 percent (n = 9) “always” see a doctor at the government
clinic when they or
Figure 27. How often do you go to the bhoua?
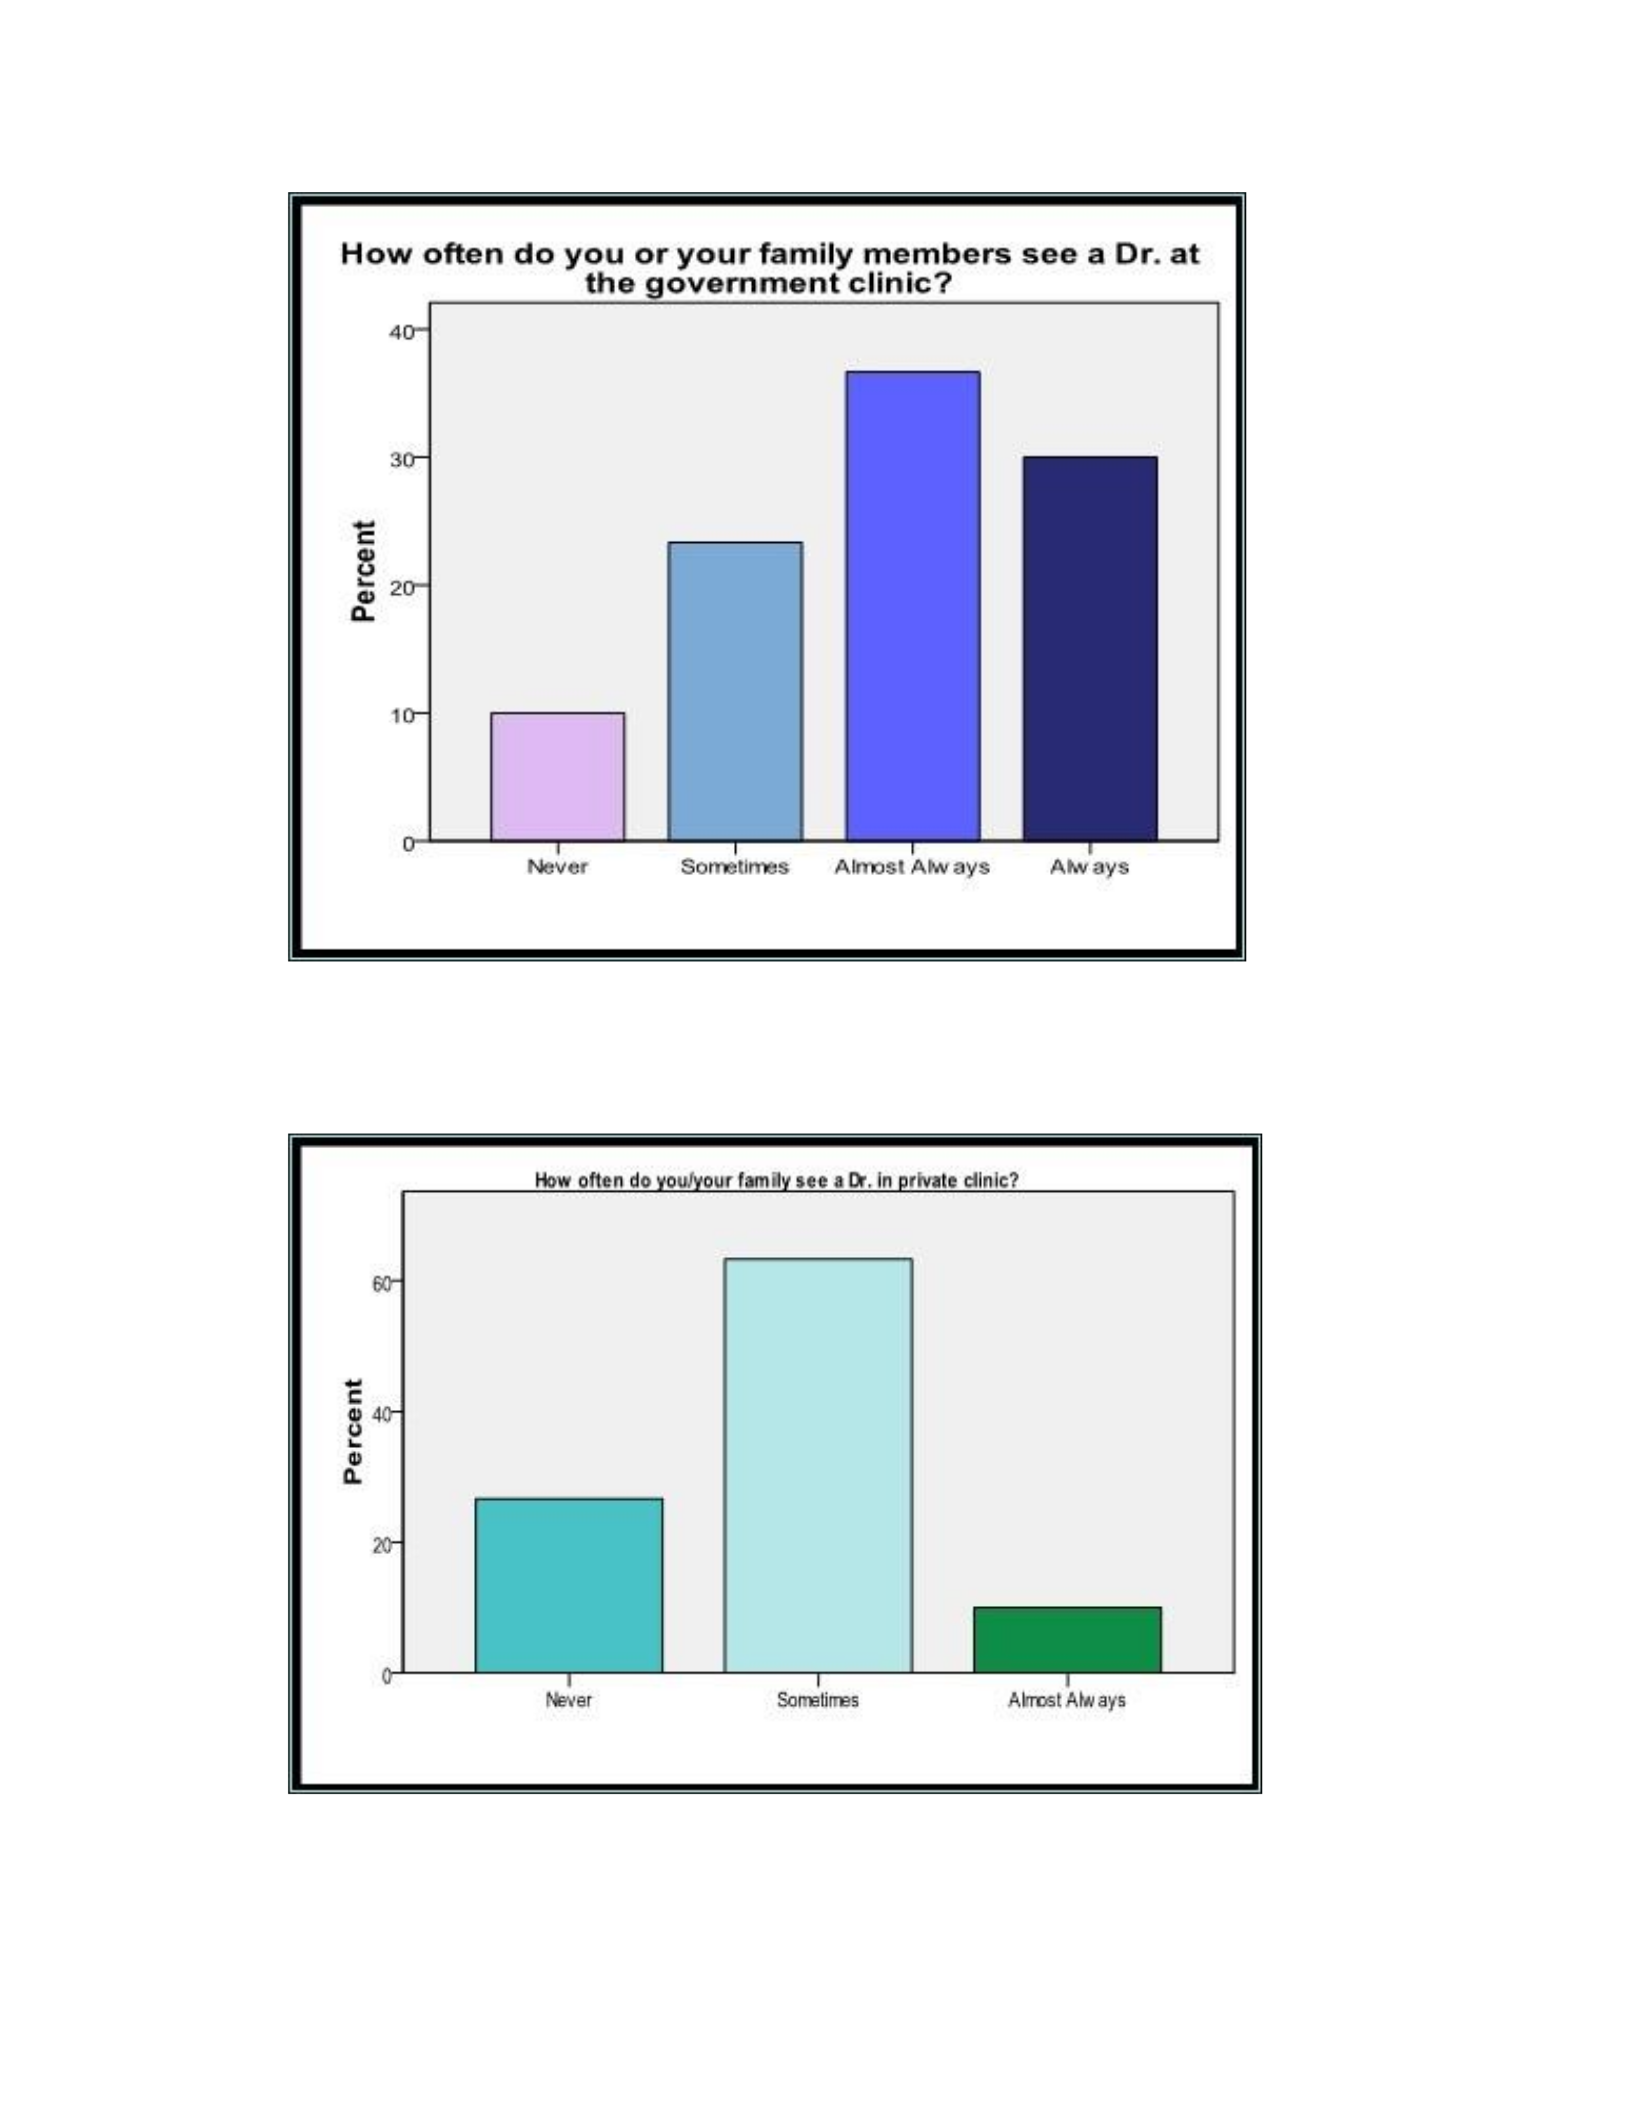
Figure 28. How often do you or your family members see a doctor at
the government clinic?

Figure 29. How often do you or a family member see a doctor in a private
clinic?
a family member is sick. Responses to the question “How often do you or your family
members see a doctor in a private clinic?” (Figure 29) were: 27 percent (n = 8) “Never,”
63 percent (n = 19) “Sometimes,” and 10 percent (n = 3) “Almost always.”
Rathwa Household Surveys
Sixty-two percent (n = 75) of household survey respondents were female, and 38
percent (n = 46) were male (Figure 30). Respondents ranged in age from 19-80 years old,
with a mean age of 37, median and modal age of 35. The number of people living in a
given household varied from 1 to 11 people (Figure 31), with a mean household size of 5.
Eighty-eight percent (n = 107) of respondents reported they were married, while 12 percent
(n = 14) stated they were widowed. Eighty-four percent (n = 101) respondents told me that
they had never attended school, while 16 percent (n = 20) had attended school, with the total
number of years of schooling varying from 0-10.
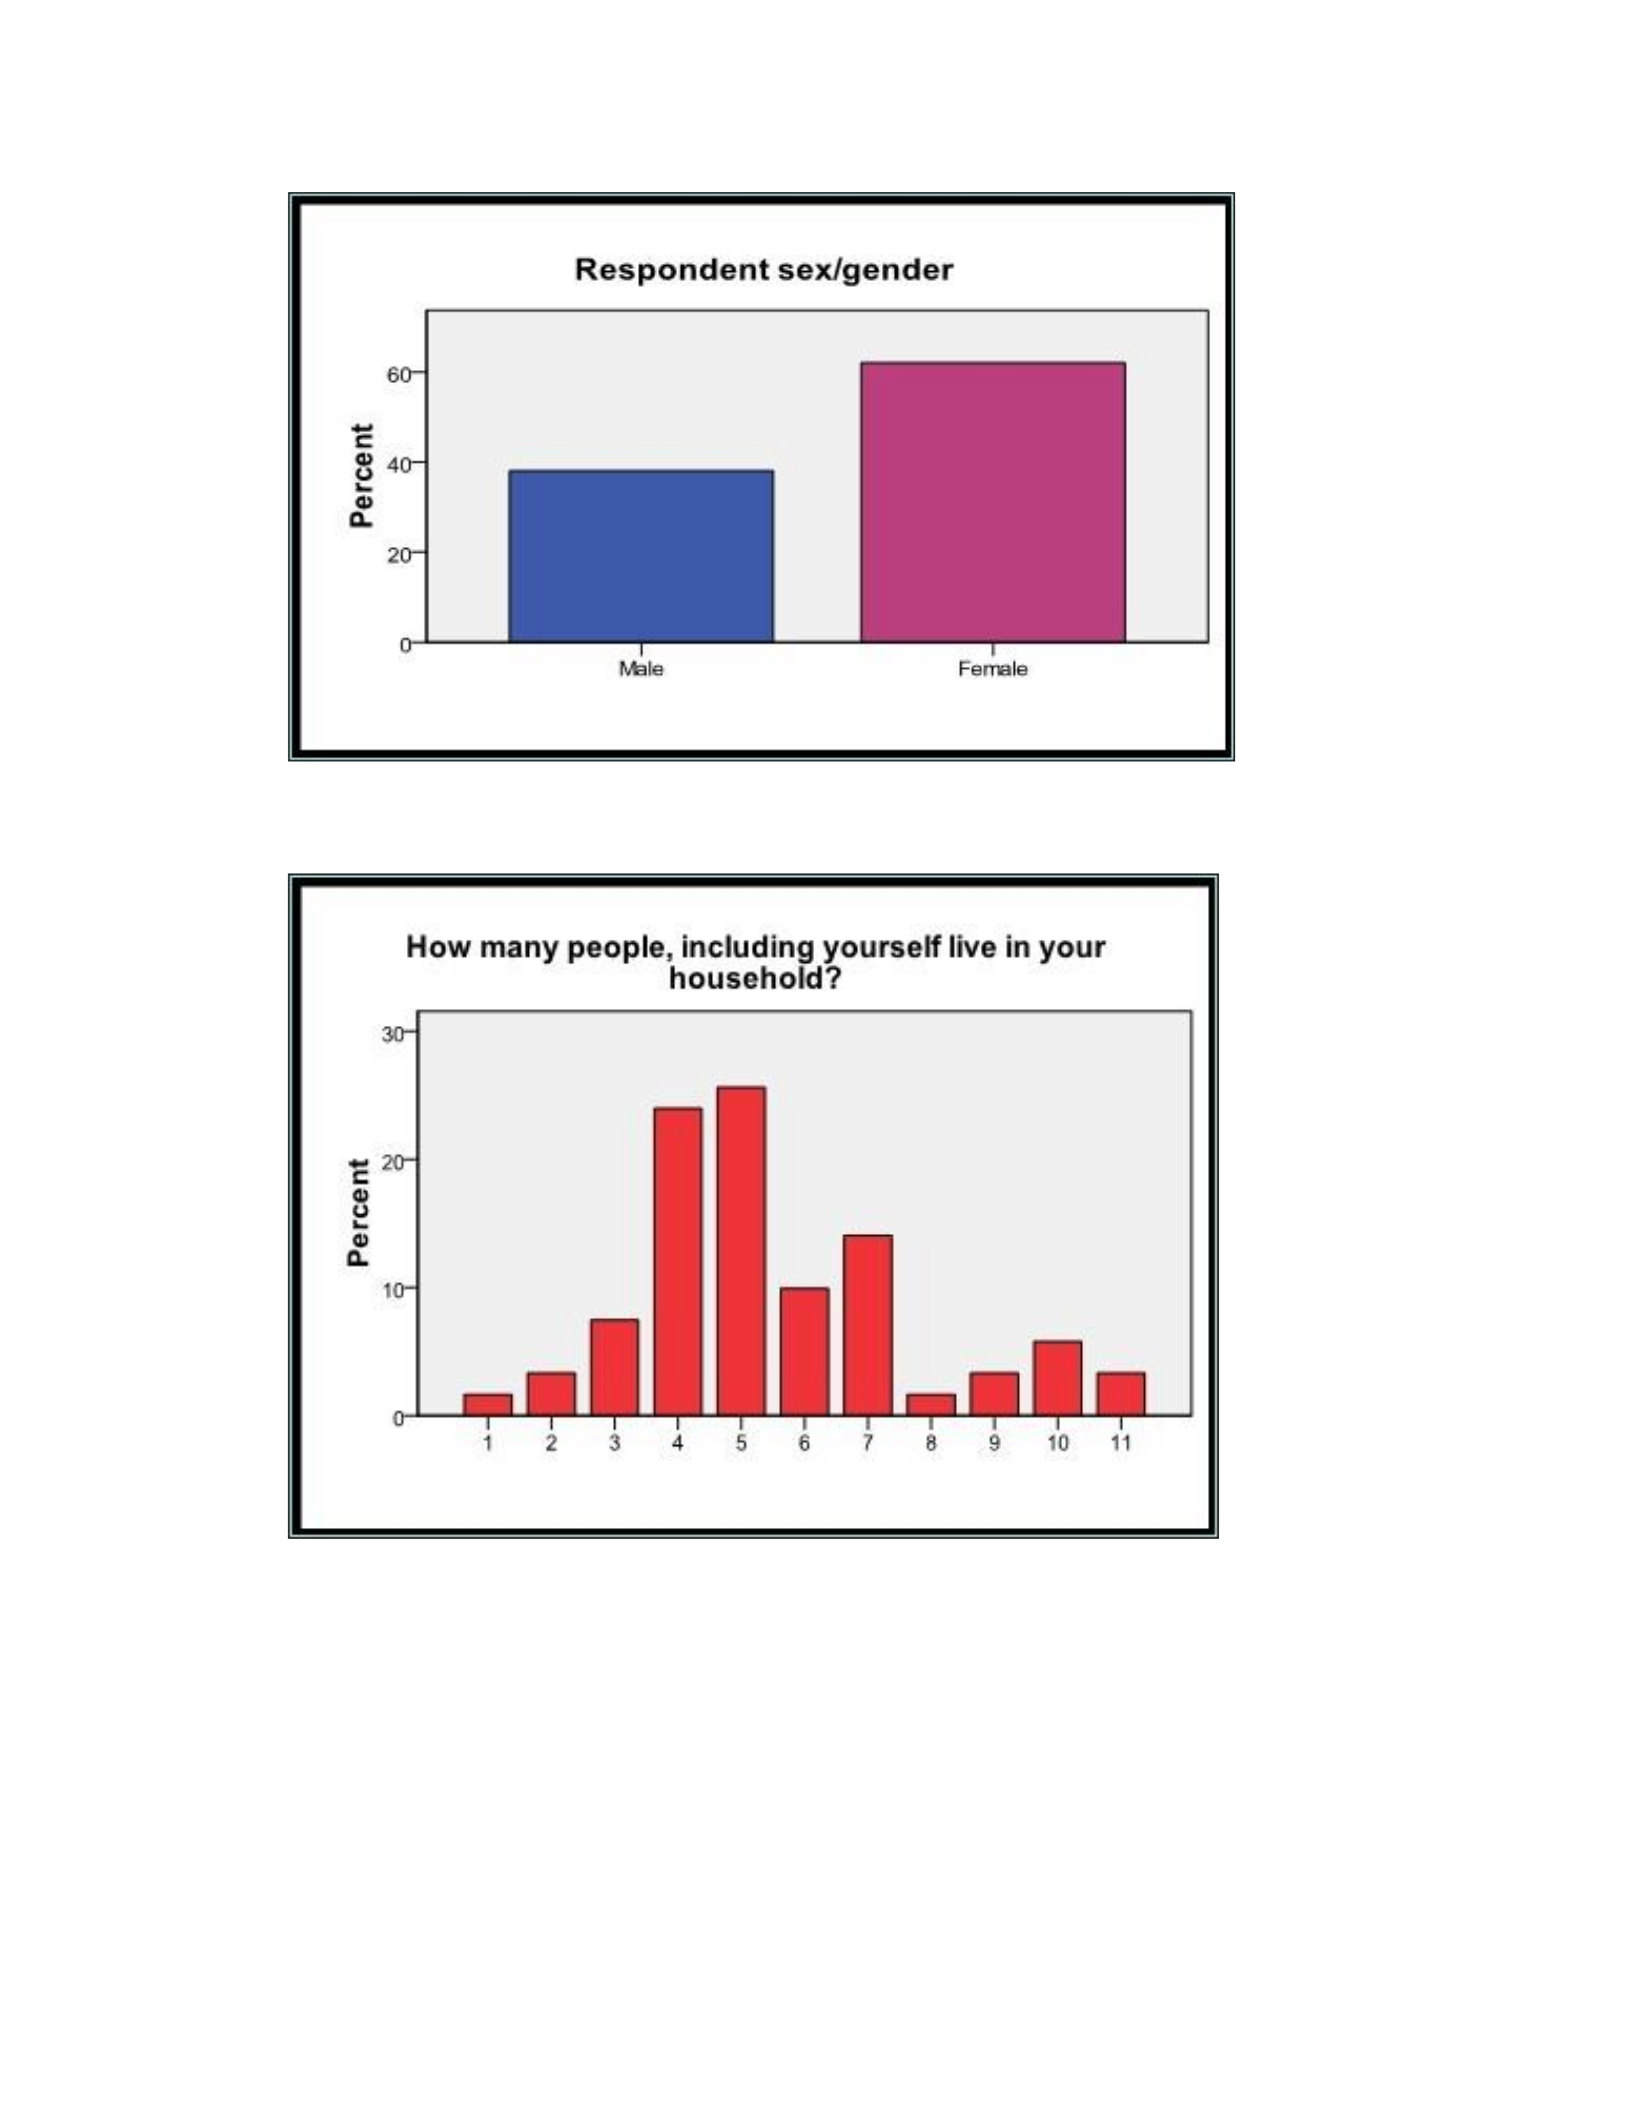
Figure 30. Rathwa household survey respondent sex/gender.
Figure 31. Number of people living in respondent’s household.
Forty-nine percent of homes (n = 59) had electricity, 88 percent (n = 107) owned at
least one chair, 45 percent (n = 55) had a table, and 98 percent (n = 119) owned a cot or

bed. The Rathwa sit on the floor to eat, so having a table or chair to take one’s meals is not
essential, though people did use chairs to sit outside the entrance to their homes and visit
with others. Nineteen percent (n = 23) had three or more livestock (e.g., cow, goat,
bullock, water buffalo, horse) and 14 percent (n = 17) owned an animal-drawn cart.
Rathwa Health Status
When asked “How good is your health?,” 3 percent (n = 4) of survey respondents
chose “Excellent,” 14 percent (n = 17) indicated their health was “Fair,” 72 percent (n = 87)
felt their health was “Good,” and 11 percent (n = 11) stated their health was “Bad.” Health
care-related decision making, one of my primary research questions, was a joint process 49
percent (n = 59) of the time, with both the head of the household and his wife deciding
together who would get what type of health care, where, and when. The head of the
household was the sole health care decision maker 38 percent (n = 46) of the time.
Respondents were also asked to rate the status of household members, with response
choices being (1) “Excellent”; (2) Good; (3) Fair; or (4) “Bad.” Very few respondents rated
the health status of fellow members of their household as “Excellent” or “Bad.” Most
stated family members experienced “Good” or “Fair” overall health, citing issues such as
poor nutrition/diet, joint pain from overwork, skin diseases, and headaches as reasons why
they chose the ratings they did.
One woman, when asked about the health of the people in her household, proudly,
beamingly, told me that her husband never gets sick. Her husband, who was nearby,
nodded in agreement and smiled. This was good news for this family, as the woman has
sickle cell disease, rating her health status as “Fair.” She had experienced a couple of

difficult pregnancies, and complained of lingering back pain since she had a Cesarean
section delivery at the public hospital. This couple had three young children, who they take
to a private clinic when they need health care, which the mother reported is infrequent.
Fortunately, this woman told me the name of the bhoua she sees for treatment, revealing
that she is the only person in the household to see a bhoua. The other family members see
a doctor at a private clinic when necessary. Throughout my time surveying and
interviewing, I noted that female respondents reported seeking the services of a bhoua, as
well as a going to a local temple, as a method of “treating” illness more frequently than
males did.
Chi-square tests showed significance between respondent sex and respondent
evaluation of health status. Males evaluated their health status higher than did females.
Sixty-five percent (n = 19) of males rated their health as “Excellent” or “Good” and 35
percent (n = 11) of females rated their health as “Excellent” or “Good.” This variation
could be due to a variety of factors, such as differential in access to health care,
reproductive health, or type of work. Women care for the family, home, and farm. Men
tend to the farm, but some are employed outside the home. If a man works for an employer
that provides on-site health care services, such as GMDC, his health status may be better
than that of females, since he has access to employer-provided health care services that
females do not.
Chi-square testing revealed significance between respondent age and evaluation of
health status. Older respondents of both sexes rated their health status lower then younger
respondents of both sexes. I expected these outcomes based on qualitative data I collected

while speaking with respondents informally and spending time with them as a participant
observer. There was no statistical significance for respondents employed by GMDC (only
males worked for GMDC) and evaluation of health status. This was unexpected as I
thought employer-provided onsite health care would result in GMDC employed
respondents rating their health status higher than non-GMDC employed respondents. Since
the Rathwa men employed by GMDC typically held labor-related jobs, it follows that the
demands of such work, coupled with the responsibilities of farm-related work at home
could make for stress on an individual’s health.
The incidence of malaria among the Rathwa is a key issue in my research, as is
sickle cell disease, a genetic condition found among populations where malaria is
pervasive. Since malaria is endemic to the region, and is considered a major health-related
problem by the Indian government, I asked survey respondents “Has any health care
provider told you that you or any person who lives here has had malaria in the last year?”
Thirty-two percent (n = 39) responded “Yes,” saying that they or someone in their
household had been diagnosed with malaria in the last year, and 68 percent (n = 82) replied
“No” (Figure 32). I was somewhat surprised at the low number of positive responses.
Most respondents appeared to know what malaria was, frequently referring to it as “fever.”
In addition, when asked about visits to the various HCPs, as well as the use of home
remedies and medicinal plants, many people indicated fever as the primary reason for using
these health-related interventions. People who stated that a household member had had
malaria in the last year were also asked about the relation of the person with malaria, their
age when they got sick, if they still had malaria, how long they had had malaria, if they
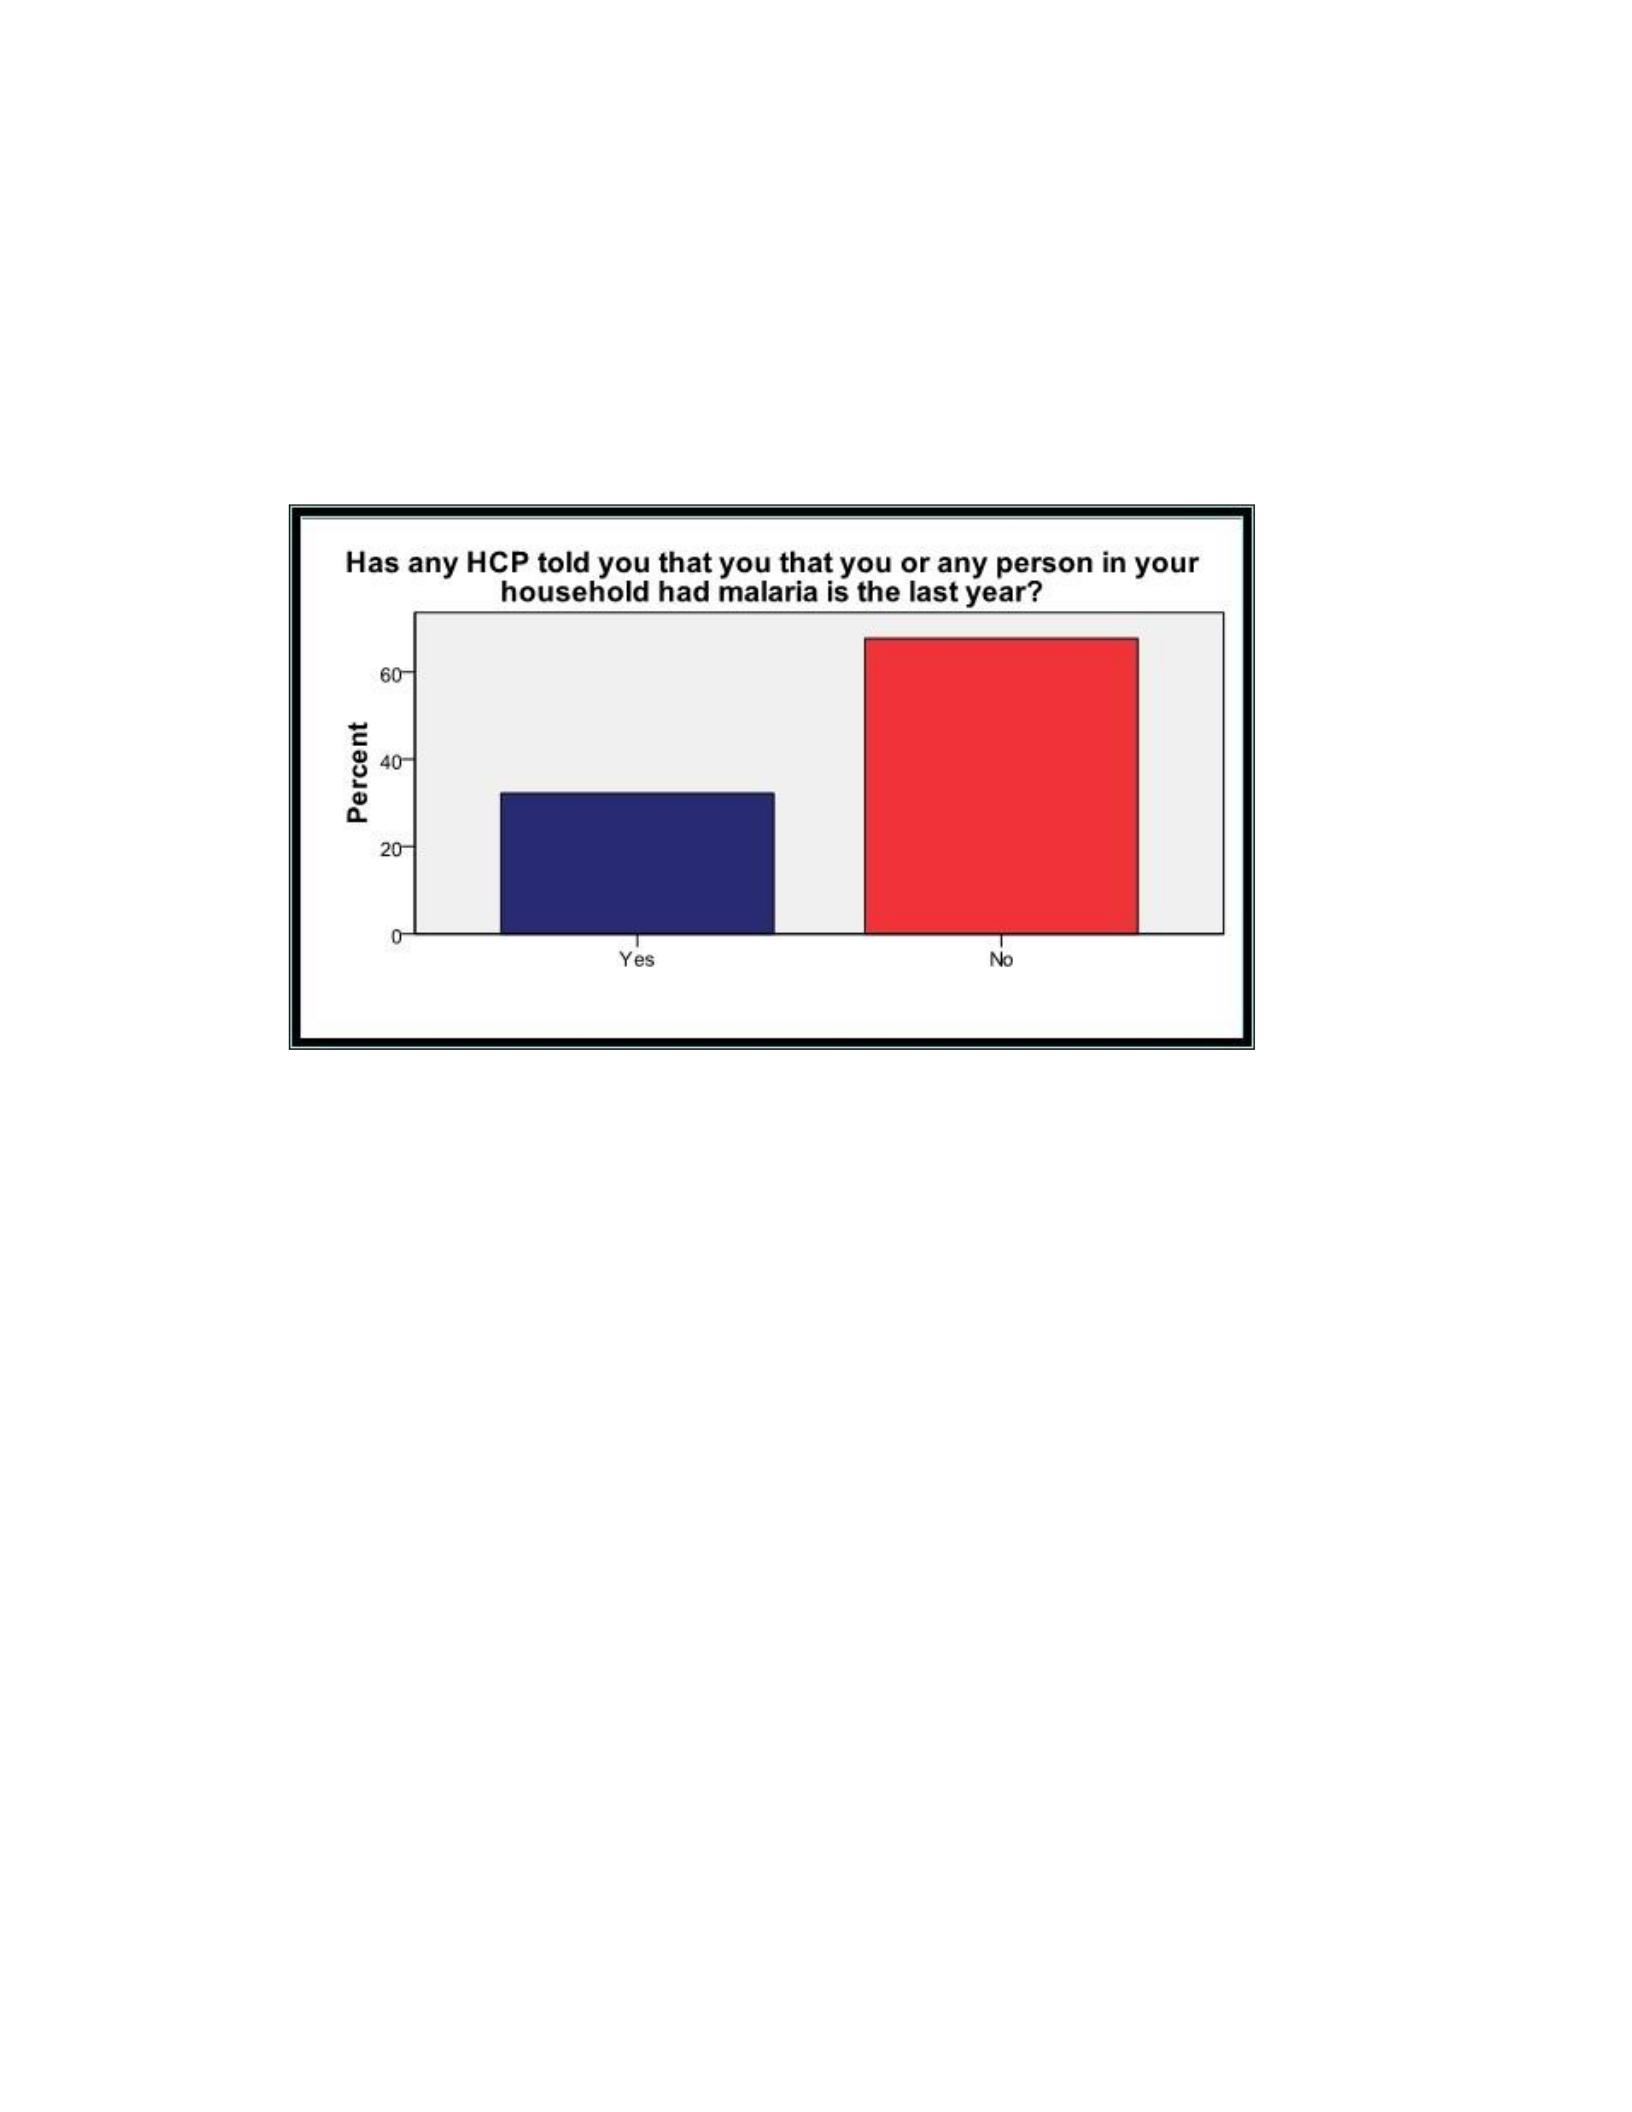
took anti-malaria medication or used home remedies, and if that person had also had
malaria within the last three years. Many people indicated that they used neem in a variety
of forms to either prevent or treat malaria. Chloroquine was the anti-malaria medication
prescribed most frequently.
Figure 32. Incidence of malaria in surveyed households.
I also asked survey respondents about the methods they used to prevent malaria,
such as sleeping with bed nets, burning mosquito coils, spraying their homes with
pesticides, using neem leaves in any manner, penning their livestock outside to decrease
mosquito attractors, covering water vessels to eliminate mosquito breeding grounds,
applying chemicals to their skin, or any other measure they might employ to repel
mosquitoes. Forty-one percent (n = 50) of survey respondents indicated that their
household does use mosquito nets when sleeping at night when they are most vulnerable to
being bitten; 59 percent (n = 71) said they do not (Figure 33). Ninety-two percent (n = 111)
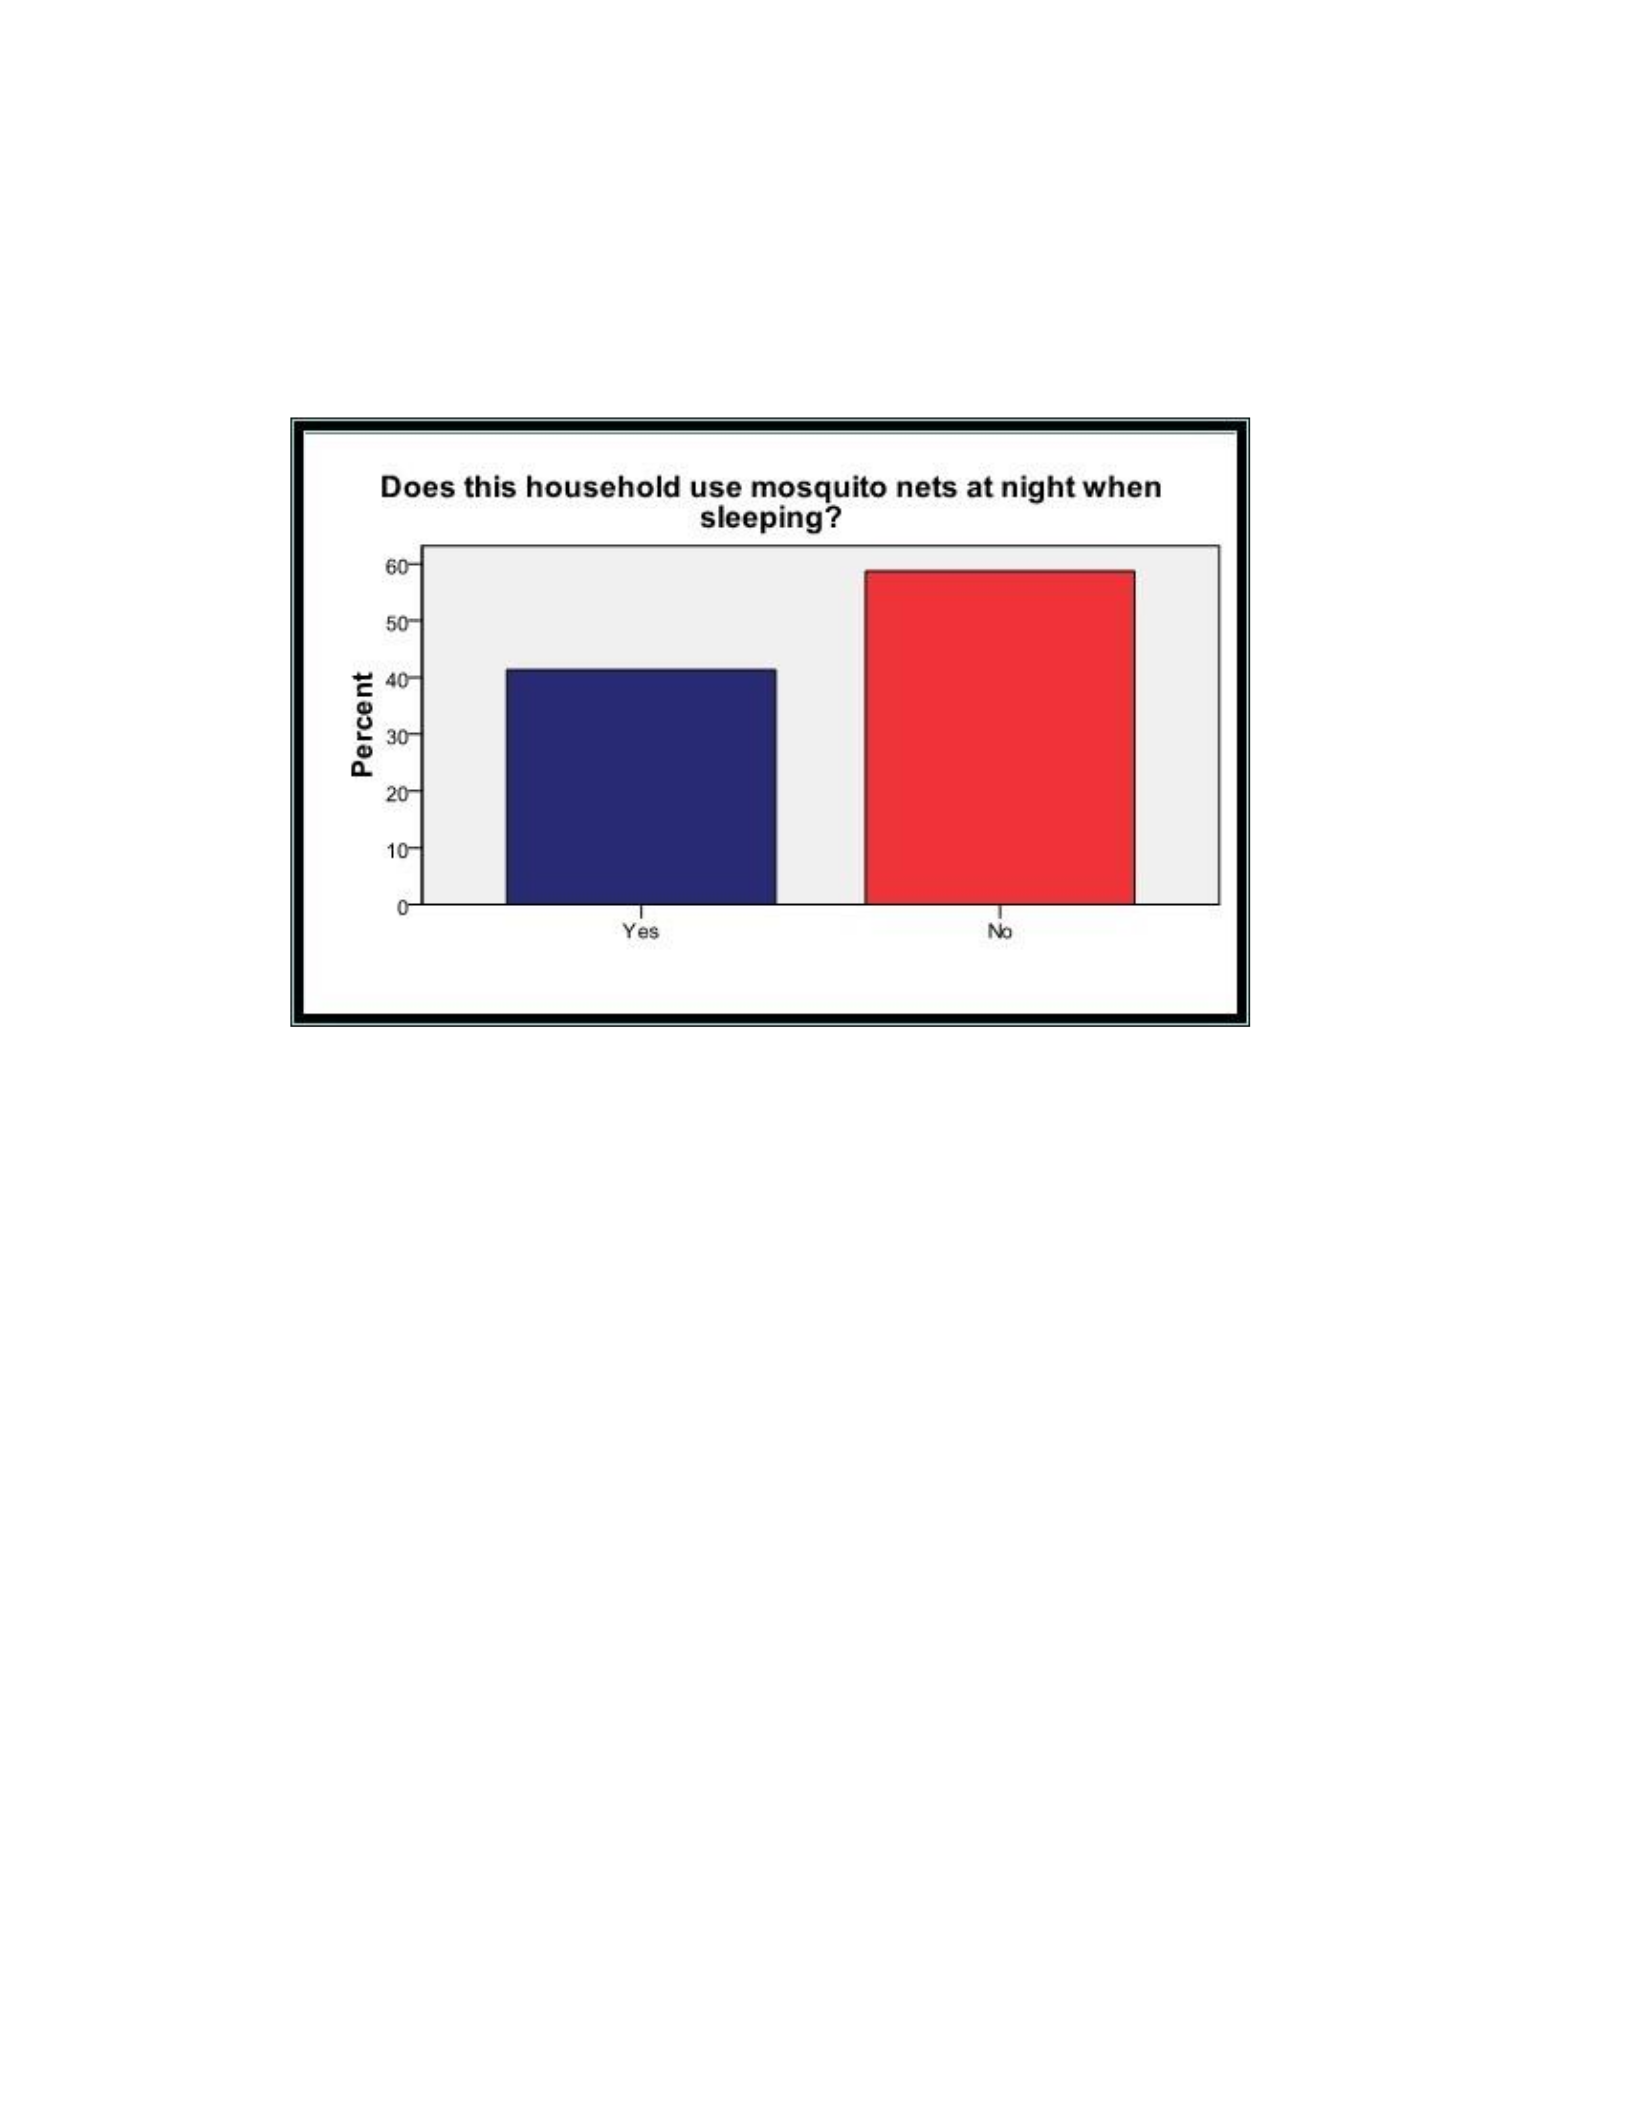
of respondents had not used a chemical spray to kill mosquitoes in the last year, while only
8 percent (n = 10) had. The village leader told me that no chemical spraying project to
deter mosquitoes had occurred in Kadipani in the last year.
Figure 33. Household usage of mosquito bed nets.
Sickle Cell Disease
Sickle cell disease (SCD) is frequently found in populations where malaria is
endemic. During my interviews and surveys, I asked questions about the incidence of
SCD, how a person who claimed he or she had SCD came to be diagnosed (e.g., while
hospitalized for crisis symptoms, or for some unrelated health issue, etc), and symptoms
they may have experienced both before diagnosis as well as during sickle cell crisis (SCC),
such as dizziness, giddiness, or joint pain.
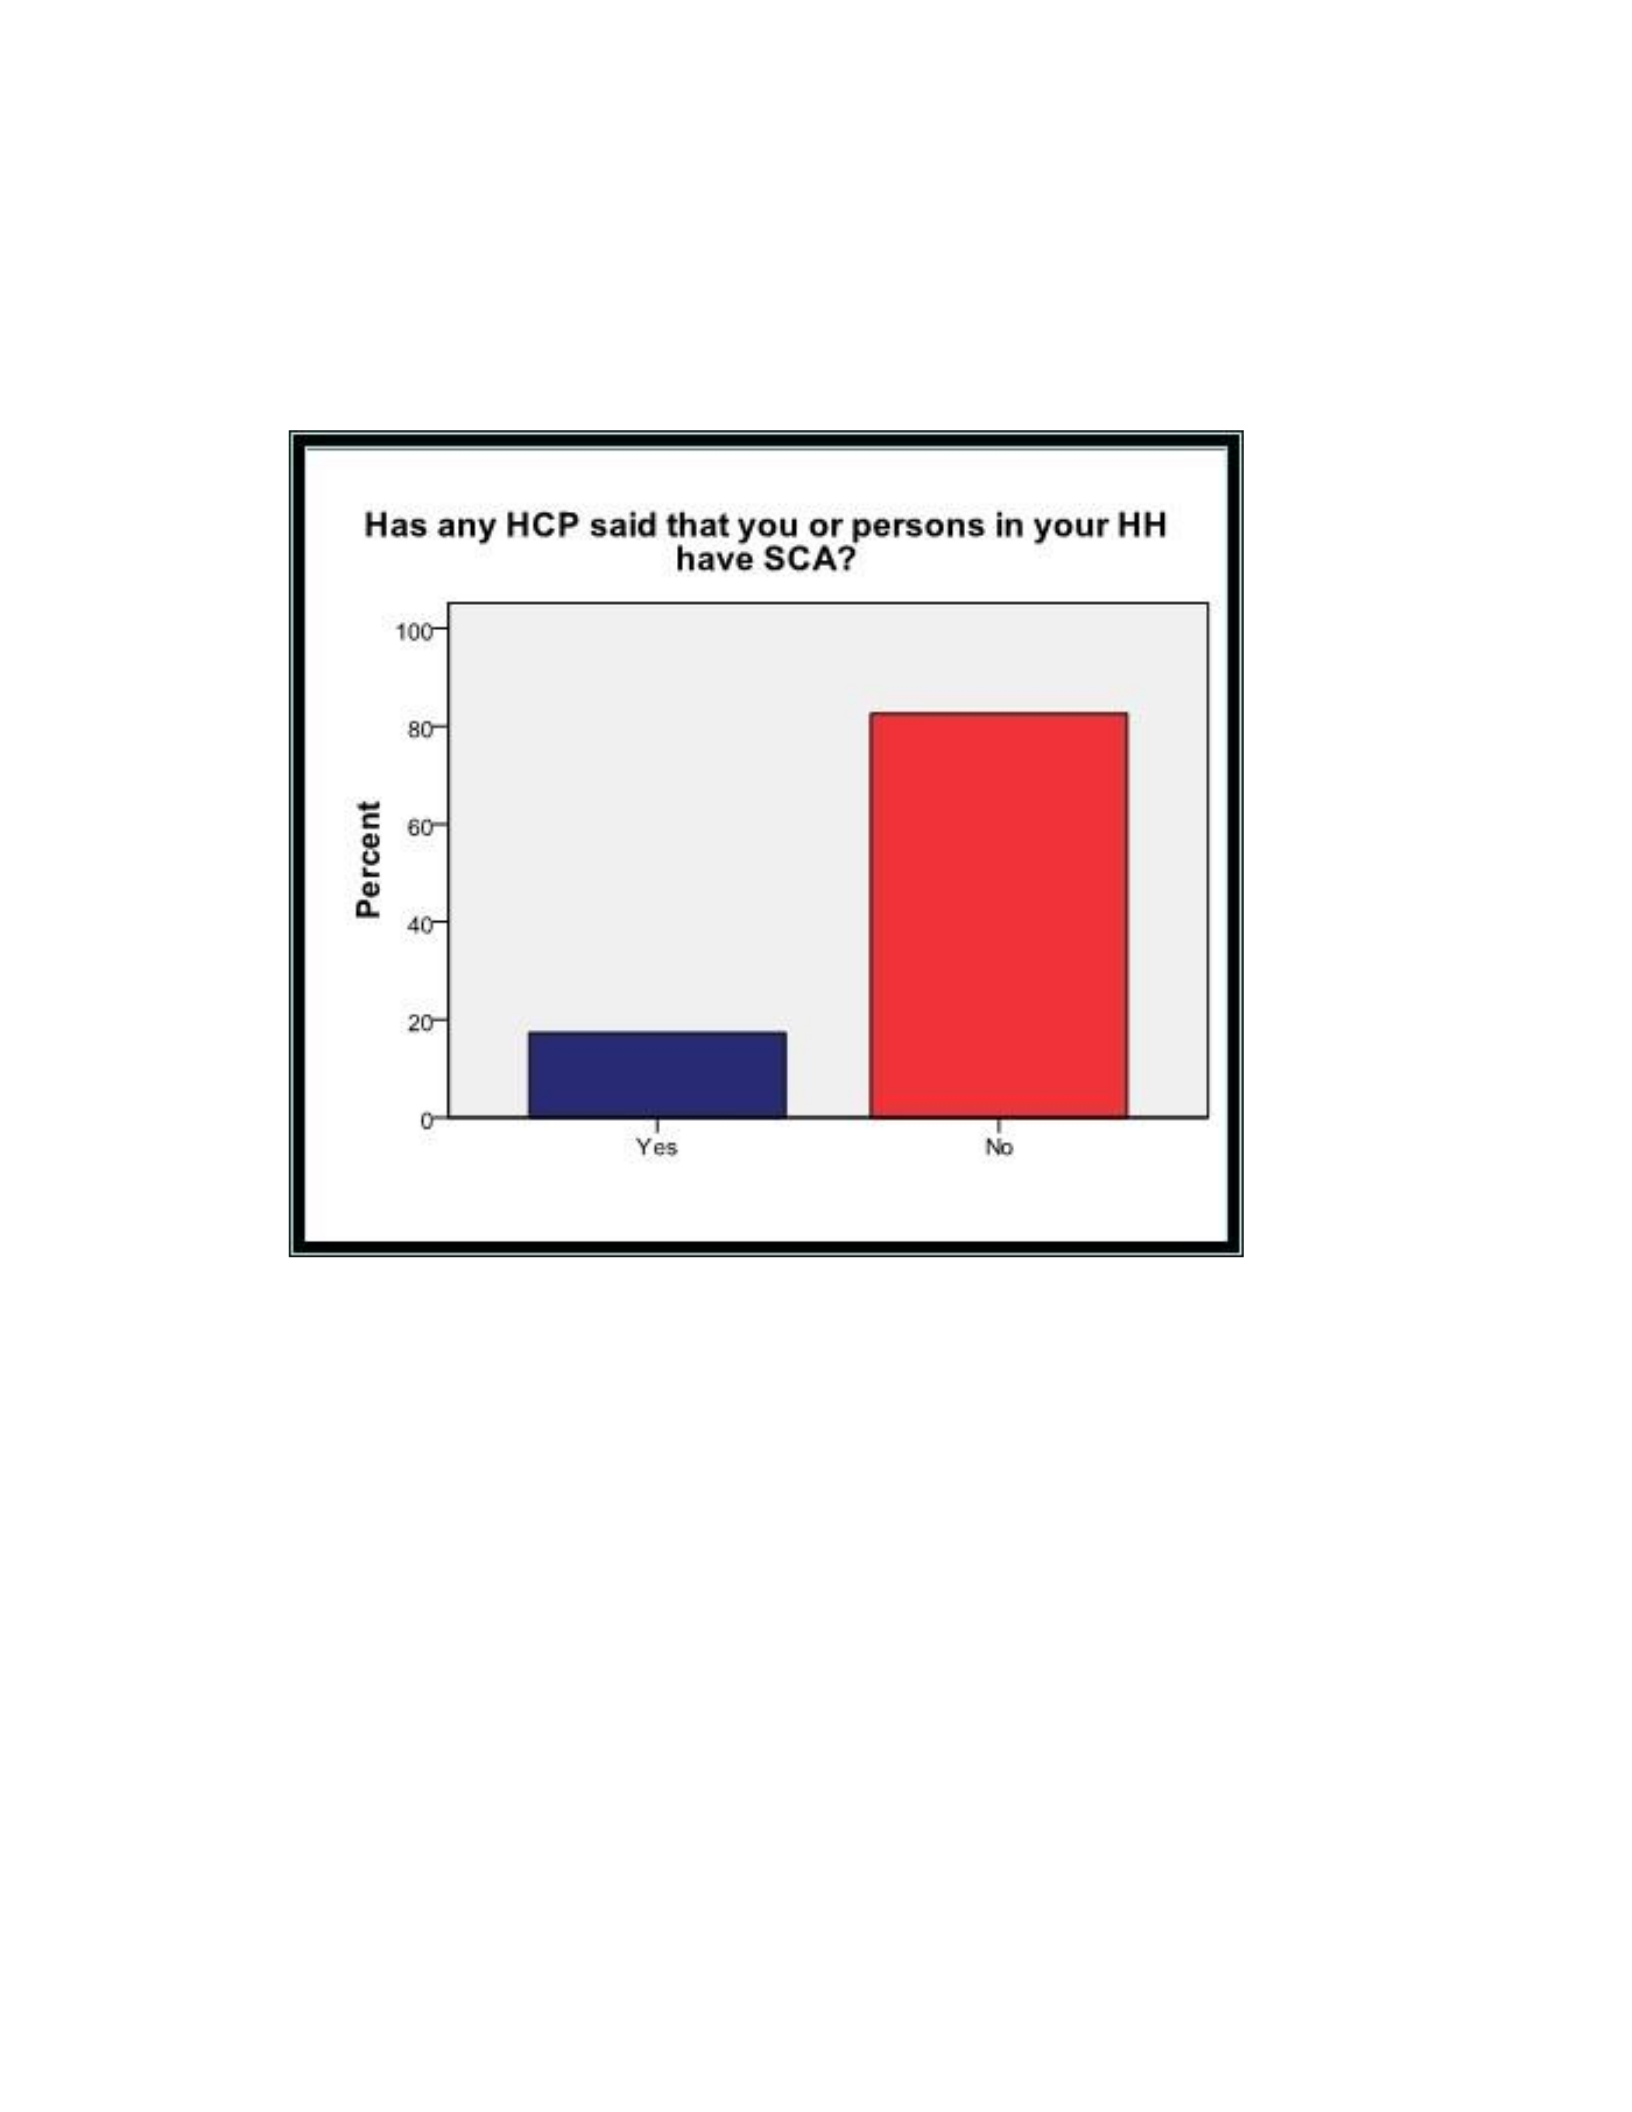
Survey respondents were asked whether any health care provider had ever
diagnosed them or a household member with sickle cell anemia. Only 17 percent (n = 21)
of households indicated “Yes,” while 83 percent (n = 100) replied “No” (Figure 34).
Figure 34. Incidence of sickle cell anemia in Rathwa households.
Barriers to Seeking and Receiving Health Care
Household survey respondents were asked about barriers to receiving necessary
health care. The question stem was: “Many things can prevent people from getting health
care for themselves or persons in their household. Indicating ‘Yes’ or ‘No,’ which of the
following are a problem when you or a person in your household wants health care?”

Respondents were asked to respond to each of the following: nine problems to getting
health care: (1) getting permission to go; (2) getting money for needed treatment; (3) the
distance to the health facility; (4) having to take transport; (5) finding someone to go with
you; (6) no female provider available; (7) no qualified health care provider; (8) concerns
that no drugs are available; or (9) physical disability or handicap.
Getting Permission and Finding the Money
Seventy-three percent (n = 88) of survey respondents indicated that getting
permission to go for health care treatment was a problem. Ninety-six percent (n = 116)
said that getting money was a problem. I was surprised that this response was so high
considering that the health care services provided by both the public clinic and hospital in
Kawant are free, as are any medications provided there. Apparently, money is a complex
issue that needs further research to explore the actual and assumed costs of getting needed
health care—not just the cost of the actual services and medications, but also all of the
other costs that add to the expense of being treated, such as paying to ride the bus, lost
wages, or less tangible or quantifiable costs, including time away from household duties
such as child care, food preparation, or tending to livestock.
Travel Companions and Female Providers
Sixty-four percent (n = 77) of respondents told me that finding someone to
accompany them to an HCP was a problem that interfered with their receiving medical
care. Only 35 percent (n = 42) of respondents felt that the lack of a female HCP was a
problem, which I found interesting because about two-thirds of my survey respondents
were female, and there were only two female HCPs practicing in Kawant, both Ayurvedic

doctors. The male medical assistant at the GMDC dispensary in Kadipani told me that he
does not handle female health-related issues, including pregnancy. Instead he has a “sister”
or “nurse” attend to those cases.
Qualified Health Care Providers, Drugs, and Disability
Only 21 percent (n = 26) were concerned about the lack of qualified health care
providers. As mentioned previously, my perception is that all health care providers except
bhouas are grouped by the Rathwa under the umbrella heading of “doctor,” regardless of
training or discipline. They referred to me as the “American Doctor,” even though I never
introduced myself as such. Possibly, my being in the company of doctors in health care
facilities made me a “doctor” by association, as well as my asking people about their health
care practices. At one point, while interviewing a family who had a 16-year-old-son who
was seriously disabled by tuberculosis of the brain, I was asked what I could do to cure the
boy. His parents and siblings looked at me beseechingly, and there was nothing I could say
that would ameliorate their pain.
The availability of drugs necessary for treating a variety of maladies was a problem
for 29 percent (n = 39) of survey respondents. Most medications are available free at the
public clinic and hospital. They are also provided free at the GMDC dispensary, and, in the
case of malaria or fever, are provided at the local fever treatment depot. The Rathwa are
exposed to a variety of infectious agents that could cause “fever,” a catch-all phrase for any
elevation of body temperature from that accompanying childhood illnesses to full blown
malaria. This was an ailment for which many people sought treatment, and which they told
me about when I visited with them. Some chose to use home remedies, such as tea made

from neem, while others preferred that the doctor provide antibiotics, especially injections.
Hardiman and Raje (2008) have also encountered this phenomenon of injections being
highly desirable, even when not medically warranted, in their work with adivasi in Gujarat.
Only 10 percent (n = 12) of survey respondents indicated that disability or handicap
interfered with their receiving health care.
I performed multidimensional scaling on the Rathwa household survey data to
determine variable clustering related to health status evaluation and health care practices.
Fifteen variables were tested in order to determine clustering of variables related to health.
Variables included: (1) sex; (2) respondent health status; (3) persons in the household
having been diagnosed with malaria in the last year: (4) household use mosquito nets at
night; (5) persons in the household having been diagnosed with SCD; (6) persons in the
household having had a blood test for SCD; (7) willingness to get blood test for SCD;
(8) visits to a private clinic; (9) visits to a private hospital; (10) visits to a public clinic;
(11) visits to a public hospital; (12) visits to a bhoua; (13) visits to a homeopathic
practitioner; (14) visits to an Ayurvedic practitioner; (15) visits to a medical doctor.
Prior to conducting my non-metric MDS analysis, I considered my hypotheses or
expectations as to how my variables might group together, as well as why. I expected to
see four clusters in the plots of my output with one of those clusters being larger. I also
expected there to be fairly close clustering in one quadrant of the variables pertaining to
malaria and sickle cell disease due to the nature of their respective topics. This did occur.

I expected that sex and health status could be anywhere in the plot, and the variables
pertaining to HCPs could be anywhere in the plot with not particular grouping. This also
occurred.
This model worked well for my dataset. The amount of stress on the model, which
is representative of how much variation there is in the model was low (.19099), and RSQ
was high (.77586). The resulting Alscal output was good. The Euclidean distance models
and scatterplots of linear fit were revealing. It helped to see my variables clearly indicated
on the plots, the distribution of the dots, which variables grouped together, and where these
clusters were located within each plot. Relationships that I suspected would be present
were present, as well as those I did not think of (Figure 35).

Figure 35. Multidimensional scaling plot for health-related variables.
Discussion of Findings
A Pluralistic System of Health Care
The impact of a society’s cultural beliefs about health and sickness on individual
and group health status is significant to the planning and provision of healing and
healthrelated services. Equally important is the process an individual or group goes
through when faced with having to make a health care decision either for him or her self or
for another. Of increasing significance is the co-occurrence of two different health care
systems, such as the ethnomedical and biomedical systems found in Kadipani and Kawant,
with multiple HCPs frequently providing services for the same patient simultaneously,
services that may at times be oppositional, and other times complementary.
The ethnomedical and biomedical health care options available to the Rathwa in
both Kadipani and Kawant make for an interesting and at times contradictory health care
system that might not always provide what people need. It appears that many of the
services provided are in response to what patients ask for, rather than being consistently
based on formal evaluation of symptoms, diagnosis, and the prescription of appropriate
treatment(s). The plurality of health care services available to the Rathwa may have mixed
short and long term outcomes. My data indicate that individuals in search of treatment
frequently access multiple health care providers simultaneously, typically being prompted
by the need for rapid relief of symptoms which affect not only quality of life but the ability
to support one’s family.

Health care decision-making was influenced most frequently by factors such as
cultural beliefs systems, local traditions, availability, cost, and convenience. During
interviews with villagers about their health care and healing practices, a majority of
respondents stressed their reliance on “tradition” or what they have always done when
faced with a particular health-related issue. One respondent told me “I go to the Bhoua
because my elders tell me to.” Typically, the Bhoua will provide his healing service and
then instruct the person to go see a doctor.
Some respondents indicated that they simultaneously receive services from multiple
HCPs, while also using locally grown medicinal plants for home remedies (e.g., neem for
malaria, ardusi for coughs and colds). In addition, many relayed that treatment for illness
may also entail praying at the temple, which was common for cases of snake bite, or when
people believed an illness was caused by witchcraft, malevolent gods, or a curse. All HCPs
were fully aware that their patients use multiple treatment modalities simultaneously, and
that the bhoua is typically the first line of defense for practically any illness. This
information was relayed to me disparagingly, with the HCPs stating that the person’s illness
could have been relieved much sooner had they not gone to the bhoua first, instead seeing a
doctor.
This phenomenon causes me to consider the role of all HCPs. When I interviewed
the non-bhoua HCPs, everyone claimed that he or she practiced allopathy. This is
prohibited by the Indian government, but it occurs for a number of reasons, most typically
because there is an insufficient number of allopaths who are willing to live and work in

rural areas, and because of patient demand for allopathic treatment options such as
prescription medications (anti-malarials, antibiotics, etc.), injections, and x-rays.
There are many traditional adivasi healing and health care practices that are
valuable and that may complement biomedical health care practices (Nayak and Babu
2003:308). Critical to such a collaborative or complementary relationship is recognition of
the benefits of various ethnomedical practices, many of which have stood the test of time,
and that could continue to be used to ameliorate sickness, when and where appropriate.
The establishment of culturally appropriate and situation or illness-specific intervention
and education programs could result in “effective need-based health care strategies” (S.
Basu 1992:15) that target problems specific to adivasi lifestyle, such as nutrition and
workrelated health issues, thereby improving quality of life while preserving dignity,
tradition and cultural practices.
The Rathwa of Kadipani village have numerous health care-related needs, some
critical and acute, others chronic. The pluralistic health care system available to them
appears to blend into one whole where all HCPs except for bhouas are considered
“doctors,” with no distinction being made among HCP disciplines or health care training
and experience. The result is a mélange of services that try to meet the needs of the
population by at times giving people the treatment they ask for whether or not it is directly
indicated by symptoms presented or formal diagnosis. This phenomenon is not atypical,
having been noted by Hardiman and Raje during their work with adivasi in Gujarat State.
They too encountered adivasi who demanded injections for a variety of illnesses, regardless
of whether or not they were medically warranted, as well as the concomitant use of

bhagats, their term for ritual specialists who use herbs, plants, and animal products to effect
healing (Hardiman and Raje, 2008:44), a healer similar to a bhoua.
There is a change occurring in health care decision making practices among the
Rathwa. This change is being prompted by two forces: (1) the people themselves who
request a particular type of treatment, such as an injection, and (2) the Indian government,
which is promoting biomedical over ethnomedical practice in many instances, such as
family planning clinics that include female sterilization procedures, polio vaccines for
children, and institutional births.
Socially Constructed Beliefs about Sickness and Health
The intent of this research was to examine both the micro and macro perspectives of
Rathwa health care and healing practices, situating these within social constructivist and
political economy theoretical frameworks. As a social constructivist, I recognize that how
individuals and groups perceive sickness and health may be complex, considering that
“well-being and suffering are experienced bodily as well as socially” (Nichter 1992:x).
Adivasi and non-adivasi groups alike have access not just to ethnomedical practitioners
such as shamans, priests, herbalists, and untrained, self-appointed healers, but also to
biomedical practitioners whose approach to health care and healing is scientifically-based
and supported by the government.
Personally held beliefs about sickness and health, as well as the quality and cost of
care, were the primary reasons why respondents chose the healing and health care systems
they did. Repeatedly, respondents told me about good as well as bad experiences with each
of the available ethnomedical and biomedical health care systems in Kadipani and Kawant.

Some respondents had very strong opinions as to the efficacy of their bhouas, the level of
concern or care shown by public clinic and hospital staff, as well as the cost of receiving
services from an HCP at a private clinic.
Rathwa socially-constructed beliefs about sickness and health, the role of
benevolent and malevolent gods and goddesses, as well as the healing powers of the
Narmada River contribute greatly to health care choices on a variety of levels. Some
respondents told me that even though they doubt the power of the bhoua, they still seek his
service anyway because it just might work. They are strong believers in the power of their
Hindu deities, and they would prefer to have a bhoua, a ritual specialist, advocate on their
behalf than to risk angering deities further, or falling out of their favor. The role of ritual in
healing and health care was evident by the numerous altars women told me they maintain
in their homes to protect their families and keep them well, as well as their explanations of
trips to local temples to pray that they or a family member recover from some illness.
Anthropology, Religious Beliefs, Healing, and Health Care Practices
The role of religious beliefs in healing and health care practices among the Rathwa
is evident from the pictures of Hindu deities hanging on the walls of the many private and
public clinics and hospital I observed, the use of traditional healers (bhouas) to evoke the
supernatural to effect healing, as well as small altars with daily offerings tucked in a corner
of many villagers’ homes, set up not only to honor and worship, but to respect and make
requests of benevolent gods and goddesses who can make sick people well when a
malevolent god of goddess has struck them. The Pithoro paintings I saw in a number of
homes, as well as 97 percent of Rathwa structured interviewees indicating that they seek

the services of a bhoua when sick, are both a testament to the Rathwa belief that the
supernatural may be called upon to heal the sick, to dispel ghosts, and to appease
malevolent gods and goddesses. It appears that regardless how health care systems may
evolve, some basic tenets pertaining to sickness and health persist because they serve some
purpose for not just the individual, but also for the community of people who hold those
beliefs.
Many cultures have “folk illnesses,” those ailments that are attributable to certain
forces, such as witchcraft, the evil eye, or some negative entity, supernatural or not, and the
Rathwa are no exception. They believe that some illness are caused by evil spirits, ghosts,
or malevolent gods, and that to remove these illness, one needs to seek the services of a
ritual specialist, the bhoua, who will advocate to a benevolent being or the supernatural.
This belief was most evident when I asked people how they treat health problems such as
snake bite or headache.
Snake bites become more common during certain times of the year when people are
outside more often, due to the need to tend to their fields. This also correlates with
monsoon season. During this time, the number of snakebites goes up, as do cases of
malaria, water-borne stomach ailments, and diarrhea. Many people told me that they called
upon a bhoua to treat them after they were bitten by a snake, or when they had head pain,
rather than consulting a doctor at a private or public clinic. In addition to seeking the
services of a bhoua for snakebite, many people, especially women, made trips to the local
temple as part of their course of treatment, not just for themselves, if they had been bitten

by a snake, but for family members who had been bitten by a snake as well. Appealing to
the gods and goddesses was a type of insurance for improved health.
The Incidence of Malaria
In retrospect, it would have been useful to ask if anyone in the household had ever
been diagnosed with malaria. This question might have yielded very different responses,
with possibly more cases of malaria within the household being reported. Some people
develop immunity to the disease if they have had it once or multiple times during their life.
However, this developed immunity is self limited, and eventually runs out. People who
have developed immunity who then move to a malaria-free area, and then eventually return
to their former community may find their immunity is no longer in effect (Sachs and
Malaney 2002). It also would have beneficial if I had asked about sickle cell disease within
families. Through this questioning, I might have been able to determine if there were any
heterozygote carriers of the HbS allele that would be afforded immunity from malaria.
Rathwa Knowledge about Malaria
While many Rathwa were aware of how people contract malaria, others did not
know there was a connection between mosquitoes and people contracting malaria.
Fortyone percent (n = 50) of households surveyed responded “Yes” when asked if they use
mosquito bed nets. During participation observation at villagers’ homes, I noticed that
some households had covered their standing water sources, such as watering troughs for
livestock, to eliminate mosquito breeding grounds. Rathwa knowledge about malaria
varied, with most people knowing what the symptoms are, some knowing how to prevent
malaria (use of neem in various forms), and where to go for treatment. Very few people

went to a bhoua for treatment for malaria, and all of the bhoua I interviewed told me that
they tell people with malaria to go to a doctor at a clinic in Kawant.
The Incidence of Sickle Cell Disease
I was surprised, for a few reasons, that my data indicated a less than anticipated
number of cases of SCD. First, during my preliminary visit in June 2007, I had held a
meeting with eight HCPs who operated private clinics in Kawant. In identifying the most
pressing health care needs of the Rathwa, they told me that SCD was a primary health
concern. Second, my sponsor, Dr. Vijay Shah, as well as other biomedical doctors I met
while working in India, told me it was estimated that 20-30 percent of my study population
were estimated to have SCD. Third, prior research on malaria and SCD show a correlation
between the endemicity of malaria and the co-incidence of SCD. Therefore, I expected that
more of my survey respondents would indicate cases of SCD in the home.
My concern is that there may have been some misunderstanding with this question.
It could be that those who have little exposure to SCD or sickle cell crisis (SCC) are just
not familiar with the disease, so when asked about it they replied in the negative. These
people live very strenuous lives, working extremely hard, and endure a lot of pain and
suffering. As stated earlier, it could be that symptoms of SCD are misinterpreted as
something else and either treated by home remedies, periodic trips to the bhoua, or
analgesics from an HCP, or they are just endured for the sake of survival.
I believe Rathwa knowledge about sickle cell disease was minimal, with many
people equating it with “rheumatism,” possibly due to the joint pain experienced by those
in sickle cell crisis. Those who knew they had SCD definitely understood the symptoms,

and frequently had stories to tell of how they were diagnosed. Many told of severe pain
in their extremities, an inability to go about their activities of daily living, and a general
feeling of malaise, somewhat like having the flu. All non-bhoua HCPs indicated that the
first line of treatment they prescribe for someone experiencing SCC is analgesics for the
pain, as well as oral supplements of folic acid, which is good for combating anemia.
When a respondent told me that he or she or a family member had been diagnosed
with SCD, I probed further for details about who within the extended family had the
disease. Typically, respondents said they were the only person in the household who had
been diagnosed. Drawing kinship charts indicating who within a family had SCD was not
fruitful. Respondents typically were not aware of who else within their families had the
disease. Young parents with children had not had their children tested, typically citing the
lack of need. If the child had not exhibited symptoms, the test was not performed.
Respondents were not aware that SCD was a genetically-transmitted disease. Most
believed it was an illness like any other, but that it lasted one’s entire life. Again, I suspect
that the symptoms of SCD, especially joint pain during SCC, was categorized by
respondents as rheumatism.
Political Economy and Health
Anthropologists most likely would agree that “human history is a demonstration
that nothing continues forever” (Axinn & Axinn, 1997:64). Raju Das (2001), in his
review essay on the political economy of India, writes of how changes over time in India,
especially those related to politics, social class, caste, and government redistribution

policies, have impacted not just the country as a whole, but also smaller entities, such as
local governments, farmers, and adivasi groups.
The agrarian nature of many parts of India, coupled with the exploitation of labor,
and the need to produce goods for various markets, creates an environment of stratification
that leaves many lacking the benefits that come from government sponsored or promoted
development efforts. Economic growth has been increasing in a number of business
sectors in India, such as high tech operations, but poverty continues to be the predominant
state of fiscal affairs for many. Those who make their living as farmers, as do the Rathwa,
may find that what they produce does not provide the needed return on investment they
have been expecting or have experienced in the past.
Social Stratification and Health Care
People I encountered throughout my time in Kadipani and Kawant seemed to prefer
to be in the company of those who were of their same caste or adivasi group. All of the
HCPs, but for the bhouas, were non-adivasi Hindus who were members of one of the four
castes: Brahmins; Kshatriyas; Vaishayas; and Shudras (S. Singh 1987:1). A caste may be
considered a self-defined social unit (Gould 1971:3) in which there is social stratification
(Singer and Cohn 1968:51) that is ascribed at birth and is life long (Singer and Cohn
1968:59).
While the Rathwa do not belong to a caste, a majority of the HCPs who provide
health care services for them do. I found there was a palpable separation of the groups,
with each maintaining their distance and operating within a previously prescribed social
role. I encountered this practice not only with the health care system, but also when I was

trying to locate someone to be my companion and translator. I was informed by a number
of different people that no one would live with me in the village because it was socially
unacceptable. This proved to be true. The reluctance of many females to accompany me to
the field because it would entail being in the presence of members of another, typically
lesser, group was at times very frustrating for me as it interfered with my ability to do my
work.
Qualified Health Care Practitioners
One factor critical to the delivery of health care anywhere is the training and
experience of the HCPs. During my research, there was only one allopathic physician
legally practicing biomedicine in Kawant village. There were a number of doctors trained
in Ayurveda and homeopathy (n = 15), all of whom responded that they practiced allopathy
when I asked them “What type of health care service do you provide?” Typically, an
Ayurvedic or homeopathic doctor would say that he or she practiced allopathy, even when
given the response choice specific to their discipline and training (e.g., Ayurvedic,
homeopathic).
I also observed non-allopathic doctors practicing allopathy, such as prescribing
medication for viral and bacterial illnesses, taking x-rays, and drawing blood for testing.
When I discussed this with my sponsor, Dr. Vijay Shah, we talked about the lack of
allopathic doctors willing to practice in the rural areas where adivasi groups live. What I
found during my work in Kadipani and Kawant is that people who are not from a rural area
are not interested in living or working in such an area—there is very little incentive to do

so, especially for female HCPs who have a husband whose career comes first. I did meet
one Rathwa Ayurvedic doctor who said he returned to the area to treat Rathwa.
Health Care Seeking Behavior and Health Care Decision Making
My initial conclusion is that Rathwa health seeking behavior is influenced by what
is learned within their cultural group (social constructivism). For example, my fieldwork
revealed that people continue to seek the services of the village Bhouas even though:
(1) many villagers openly acknowledge that the Bhoua does not have the ability to heal,
and (2) many diseases are self limiting and resolve by themselves. The coincidence of a
visit to the Bhoua with symptomatic improvement may reinforce the belief that the Bhoua
actually has supernatural healing powers. But, coincidence does not imply correlation. As
told to me by a number of villagers, Rathwa seek the services of the Bhoua because of
“tradition,” that is what is done, so they do it.
Similarly, some patients will tell the doctor specifically what treatment they prefer
(injections, antibacterial washing of an injured area even though it is not medically
warranted), possibly because it has worked for them or a family member in the past. The
patient’s intent is to regain health so as to return to the work of caring for families and
earning a livelihood. In this case, one’s personal economic situation, as well as the local
economy, are driving forces behind health care decision making and healing practices.
Worthy of consideration is the impact of modernization on health care decision making,
especially with the increasing mobility of people from remote villages to cities in search of
treatments and cures.

Also, the role of the Indian government in the promotion of certain health care
practices such as vaccination programs for children, institutional births instead of home
deliveries, and prevention of diseases such as malaria via education programs, may move
the population toward a more biomedically-based system of health care, resulting in the
modification and possibly the abandonment of age-old cultural practices, such as
indigenous healing methods and religious belief systems (personal conversation with
Kawant government hospital medical director, June 2007). With a relatively broad
continuum of health care services available, the intersection of ethnomedical and
biomedical health care practices may impact household health care decision making,
possibly resulting in conflict with Rathwa history, tradition, and cultural practices.
The data discussed in this chapter reveal that indeed there is a change occurring in
how the Rathwa make health care related decisions. Primarily descriptive, the data
reinforce the position I stated earlier—that there is a rift between traditional and modern
health care practices. This tension has led to people rethinking their health care options.
Respondents frequently expressed dissatisfaction with the quality of health care they have
received in the past, regardless of the discipline of the HCP, and, based on prior experience
they or a family member had had, were prompted to request specific treatments, even
though the treatment requested was not necessarily the treatment of choice for the ailment
they were experiencing.
Issues related to access to services as well as treatment cost were prime factors that
determined where and when people sought help. A common theme, whether I was
interviewing HCPs or villagers, was that the role of the bhoua was in flux. Many people,

both villagers and HCPS alike, made disparaging remarks about the bhouas, doubting
their ability to heal, and considering them to be “cheats”; “Not really able to help
anyone”; “They cause illnesses getting worse because they cannot treat it effectively”;
“The community decides where you go first—the elders say you go to the bhoua so they
go.
When they don’t get better they come to see a doctor.”
The bhoua operates from a position of faith, both his own in his ability to intercede
with the supernatural on behalf of his patient, and the patient’s belief in the same. The
bhoua’s ongoing existence is dependant on this faith remaining vital, rather than dying out
and possibly being replaced by less traditional/ethnomedical practices. It is not possible to
be half hero and half charlatan, and it appears that many Rathwa feel this way about the
bhouas. While bhouas may continue to have a place in the continuum of health care and
healing practices among the Rathwa, it is possible they may be relegated to the position of
cultural artifact, something that served a purpose at one time, but that now has limited use.
GMDC and the Local Economy
GMDC employs some Rathwa men in a variety of jobs, such as laborers, security
guards, welders, and truck drivers. Rathwa employed by GMDC have economic and health
care advantages that non-employees lack. During my research I learned that households in
which a member worked for GMDC had higher monthly income, had more items indicative
of higher socioeconomic status (e.g., scooters, furniture, cell phones), and had access to
GMDC-provided health care services at the workplace, including treatment for malaria.

As both a medical anthropologist and a development anthropologist, I see in the
case of the Rathwa that “development has powerfully modified the individual’s everyday
life” (Cernea, 1995:340), evident with the GMDC mining operations and concerns about
damming projects along the Narmada River. Those who responded to my household
surveys who worked at GMDC had access to health care service staffed by biomedical
doctors at the mine operation site, and a higher income with which to make choices.
During my preliminary visit to Kadipani in June 2007, the GMDC plant was offline—it had
not been operational for quite some time due to renovations and upgrades being made at the
site. Rathwa men who had worked for GMDC prior to its furlough had to rely on other
sources, typically farming, for income for their households. The mine was in full operation
when I arrived in Kadipani in November. Very shortly after the mine resumed operations,
the workers called a strike.
As I took my morning walk to the temple prior to beginning my work that day, I
heard loud music, horn blowing, drum banging, and saw men sitting on the ground outside
the entrance to the mine site. I spoke with some people at the GMDC guesthouse where I
was staying and asked what was going on. They said “strike” in English, a concept
universally understood, and that was it. I ventured down to see what was going on. The
mine had only recently resumed operations, so I wondered what could have happened to
bring production to a halt so soon. How would this work stoppage affect the village and
the Rathwa that worked for GMDC? No one I asked had a clear answer as to what was

going on and why. The next day I was told the labor dispute had been resolved and the
men returned to work. There were no further labor strikes during my time in Kadipani.
While living at the GMDC guest house, I met a young doctor who was completing
his medical rotation at the GMDC plant medical clinic. We spoke at length about the
illnesses he most frequently treated GMDC employees for, as well as general health issues
of the local population. This doctor had access to medical equipment and supplies not
found at other biomedical health care facilities in the local area. GMDC employees who
were experiencing health problems could visit the clinic, see a biomedical doctor, receive a
diagnosis and be treated. No travel or money was involved. Absent were the long lines
one might experience while waiting to be seen by a biomedical doctor at the government
clinic in Kawant. The relative ease with which GMDC employees could receive medical
care and treatment outstrips that of the biomedical facilities in Kawant.
While GMDC is providing employment, income and local development for the
people of Kadipani, it is also contributing to changes in perceptions about traditional and
modern health care practices. When a GMDC worker receives a treatment at the GMDC
medical facility that is not available at any other local health care facility, a dichotomy
develops. Equity in the provision of health care shifts—some have access to services,
others do not. This disruptive effect impacts locally held beliefs about what is traditional
and what is modern. With the continued introduction of more modern health-related
services, people may increasingly question the validity of their traditional practices and
practitioners, such as bhouas.
Conclusion

One can never be completely prepared for what might transpire while in the field.
This is what makes ethnographic research interesting, dynamic, and an experience far
beyond what may have been imagined in one’s mind or written about in a dissertation
research proposal. The reflexive nature of anthropology adds a dynamic to the research
process that may not be found in other disciplines that study humanity. When I entered the
field, I went with the expectation that I would explore in depth the health care decision
making process employed by the Rathwa. I was going to address my research questions
and find out what I wanted to find out. While those were my intentions, once in the field,
things took a slightly different turn.
I imagined that Rathwa health care decision making would be a rather black and
white process in that someone either went to an ethnomedical or biomedical health care
provider, and that there would be an every growing trend away from ethnomedicine toward
biomedicine. This was not the case for everyone. Yes, some people were forgoing visits to
a bhoua because they saw little reason to continue when they did not get better. Others did
not have the funds to pay for health care so they always went to the government-sponsored
clinic or hospital, which were free. Still others were not satisfied with the quality of care
received from the government facilities and chose instead to seek the services of private
health care providers on a fee-for-service basis. And, there were a few people who never
went to any HCP but for the bhouas, as they did not trust “doctors.”
My expectation that modernity or modernization would be the driving force behind
any change in health care and healing practices was tempered by my belief that people
would hold true to their belief systems about what causes sickness and what restores health.

I also knew that the availability of funds within a household would be a strong determiner
of who received what type of health care and when. It was up to me to reconcile all of
these variables in my mind, and while keeping my Western-focused bias in check, come to
a conclusion as to what drives people to make the health care and healing choices that they
do.
CHAPTER SEVEN
CONCLUSIONS AND RECOMMENDATIONS
Introduction
This chapter presents the conclusions I have drawn from my research, a discussion
of my five research questions, as well as recommendations for follow up research and
program development.
Main Conclusions
Anthropology has a lengthy history of involvement in issues relating to “social
and cultural change” (Hoben 1982:349) across the world. Much change has taken place
in the field of health care in India over the years, reaching into rural locations as well as
major metropolitan areas. In India, as elsewhere, there may be multiple treatment
approaches, ethnomedical as well as biomedical, for any one sickness or disease. How a
health care recipient or other health care decision maker arrives at a choice of treatment,
or a combination of treatments, is culturally-based, and tied to local beliefs about health,
healing, and sickness (Basavanagouda 2004; S. Basu 1992; Langford 1999; Nayak and
Babu 2003; Tyagi 2002). I found this to be the case with the Rathwa of Kadipani, who

repeatedly told me that they do what they do when it comes to health care choices
because they have always done it that way, it is what they believe, and it is their tradition.
Health, which has been defined by the World Health Organization as, “a state of
complete physical, mental and social well-being and not merely the absence of disease
or infirmity” (WHO 2007, emphasis added), seems to be more elusive for some people
than others, and possibly not attainable at all, depending on how one conceptually and
operationally defines “complete.” So many variables affect the health of individuals
and families, as well as entire communities. Out of widely varying concepts of sickness
and health have come numerous health care and healing practices, some religious or
faith based, others grounded in empirical science.
Of late, increased attention has been paid to “Western” systems of health care and
healing within the context of choice and health care decision making (Garro 1998a,
1998b, 2000), and how various cultures throughout the world make differing
healthrelated choices and why. Kleinman and Kunstadter observe that health care and
healing systems are pervasive, being “found in all known cultures, but their variety is
enormous” (Kleinman and Kunstadter 1978:1). It may be the variety of healing and
health care practices found throughout the world that anthropologists find so fascinating
and compelling to study, using the comparative approach that is so unique to
anthropology.
India, a country of approximately 1.12 billion people (CIA 2007), with a history
reaching back 5,000 years (Walsh 2006:xiii), has developed, over time, a number of
indigenous and scientifically-based health care and healing methods, some of which are

available to the Rathwa. Partner these healing and health care systems with Rathwa
beliefs that some sicknesses are caused by evil spirits, ghosts, witchcraft and sorcery, and
the result is a need for an approach to health care and healing that is holistic,
compassionate, and effective, while being respectful of culture, history, and tradition.
Section I: Research Questions
The Five Research Questions
My intent with this dissertation research was to address five research questions
related to Rathwa health care and healing practices:
1. What prompts the Rathwa to seek a certain type of health care, be it
ethnomedical, biomedical, or a combination of both?
2. Do Rathwa forgo ethnomedical practitioners and instead visit a biomedical
practitioner when faced with disease or illness? If so, what factors influence
this decision?
3. If there has been an increase in Rathwa accessing biomedical services, which
diseases most frequently result in visits to biomedical practitioners (e.g.
malaria, sickle cell disease, fevers, childbirth, broken bones, etc)?
4. What impact do traditional gender practices have on health care decision
making?
5. What is the impact of economic development projects in the region where the
Rathwa live on adivasi health care decision making, especially as it relates to
household income and socioeconomic status?

The data I collected during my time with the Rathwa and the HCPs in both Kadipani and
Kawant shed light on these questions. There were no surprises, just some instances of
clarity as well as the reinforcement of some expectations.

