


CHAPTER 1: INTRODUCTION
The World Health Organization (WHO; 2019) defines comprehensive sexual health as
well-being across physical, mental, and social domains. With that, comprehensive sexual health
“requires a positive and respectful approach to sexuality and sexual relationships, as well as the
possibility of having pleasurable and safe sexual experiences, free of coercion, discrimination
and violence” (WHO, 2019, p.1). However, to date, much of the sexual health research has
focused narrowly on the absence of disease and unintended pregnancy (i.e., physical domains)
rather than all of the other comprehensive aspects described above (WHO, 2019; Zielinski,
2013). Accordingly, most of the sexual health information we know is about disease and
unintended pregnancy (Zielinski, 2013). For example, although global data is limited, when
compared to other industrialized countries (i.e., France, Germany, Netherlands) the United States
is one of the least sexually healthy (Advocates for Youth, n.d.). In 2009, the United States had
HIV/AIDS diagnoses that were six times higher than those in Germany, three times higher than
those in the Netherlands, and one and a half times higher than those in France (Advocates for
Youth, n.d.). Further, best estimates suggest that approximately 50% of all sexually active people
in the United States will acquire some type of sexually transmitted infection (STI) by the age of
25, which is significantly higher than other industrialized counties (ASHA, 2019). For example,
estimates suggest that in the United States there were more than 1.7 million Chlamydia
diagnoses in 2017 (CDC, 2018). This is approximately four times higher than the number of
Chlamydia diagnoses in the EU/EEA in 2016 (ECDC, 2016). Additionally, the United States has
more unintended pregnancies than any other industrialized country (Advocates for Youth, n.d.;
Guttmacher Institute, 2019). For example, in 2006 the US had more than four times the number
of teenage pregnancies than the Netherlands (Advocates for Youth, n.d.). Taken together, and
compared to other industrialized counties, the United States appears to host poorer levels of
physical sexual health, thereby, warranting further examination of this public health concern.

Importantly, not all individuals in the United States are at equal risk to experience
negative sexual health outcomes. Specifically, individuals who have at least one minority status
(e.g., women, racial or ethnic minorities, LGBTQ+, individuals with low SES) are more likely to
experience poorer sexual health outcomes when compared to the majority (CDC, 2017b;
ODPHP, 2019). These are known as sexual health disparities (CDC, 2017; ODPHP, 2019). Two
of the most vulnerable groups that experience sexual health disparities are queer individuals
(LGBTQ+; National LGBT Health Education Center, 2016) and women (CDC, 2011).
Additionally, queer women (also referred to as women who have sex with other women; WSW;
CDC, 2015) are significantly more likely to be diagnosed with Human Papilloma Virus (CDC,
2015) and Herpes Simplex Virus (HSV-2) when compared to women who engage in different
gender sexual relationships (CDC, 2015). Finally, approximately 1.1 million cases of chlamydia
were diagnosed in women (regardless of their sexual identity) in 2017 (CDC, 2018). Thus,
sexual health disparities among these groups are evident.
Because research has examined health disparities as the presence of disease diagnosis (as
listed above; Zielinski, 2013), the primary disparities we know about are the presence and
absence of disease. By minimizing sexual health to disease diagnoses, the field has overlooked
myriad ways that indicate someone’s sexual health, foregoing further insight into other potential
sexual health disparities (Zielinski, 2013). Although there is not much research on other
indicators of sexual health (e.g., sexual pleasure such as orgasm, sexual functioning, feelings of
safety, feelings of sexual anxiety or depression), research does broadly suggest that disparities
exist across these indicators. For example, there are significant gaps in rates of orgasm between
heterosexual men and women when engaging in penetrative sexual intercourse (Kinsey Institute,
2019). Additionally, heterosexual women are significantly more likely than heterosexual men to
experience shame, depression, and guilt about their sexuality after engaging in casual sexual
behavior with another person (Allyn, 2000; Garcia, Reiber, Massey, & Merriwether, 2012).
Queer women are more likely than their heterosexual counterparts to experience sexual assault,

rape, or violence (i.e., 61% of bisexual women, 44% of lesbian women compared to 35% of
heterosexual women; Human Rights Campaign, 2019) leading to lower perceptions of safety.
Therefore, by attending to these already conceptualized, yet understudied, comprehensive
domains of what sexual health is, we may be able to gain more insight into sexual health
disparities in vulnerable groups, such as queer individuals and women.
Determinants of Health and Sexual Health Disparities
Another important line of inquiry focuses on identifying the factors and processes
involved in the creation and persistence of sexual health disparities. The Determinants of Health
Framework (DoH), created by the World Health Organization, examines how policymaking,
social factors, health services, individual behaviors, and biology/genetic makeup lead to health
disparities (ODPHP, 2019). Importantly, these determinants examine more than just disease
because they examine how social factors can contribute to who is healthy and who is not. By
taking a DoH perspective toward sexual health (WHO, 2010b), we can examine sexual health
disparities beyond medical diagnoses of STIs and unintended pregnancies. For example, a queer
person may not have an STI (which traditionally would be perceived as sexually healthy), but
may experience cultural discrimination because of their sexual identity (Meyer, 2003). The
discrimination they experience may be internalized, leading to poor physical and mental health
outcomes (Meyer, 2003). Thus, even though the individual may be physically healthy (i.e. they
do not have any STIs), the experience of cultural discrimination still contributes to disparate
health outcomes (WHO, 2019). Accordingly, the DoH framework helps to broaden the analysis
of sexual health disparities and provides a deeper examination of the social factors that
contribute to these disparities.
A particularly understudied contributor to sexual health disparities is culture. Culture
includes the beliefs, values, systems, and practices in which someone develops, that are socially
constructed and enforced (Ratcliff, 2017). More specifically, scant research has examined the
impact of heteronormativity on comprehensive sexual health disparities. Heteronormativity is a

cultural norm which privileges individuals who are heterosexual, monogamous, and only have
sex inside the confines of marriage (van Eeden-Moorefield, 2018). This norm started from the
Puritan era push for sexual morality which sought to suppress sexual desire outside of marriage
and limited sexual interactions to those for the purposes of reproduction only (Easton & Hardy,
2009; D’Emilio & Freedman, 2012). Messages about sexuality included demonizing
masturbation, same-gender relationships, and shaming forms of contraception and birth control
(D’Emilio & Freedman, 2012).
Importantly, heteronormativity does not appear to have a direct effect on health
outcomes, but instead, it exudes an indirect effect on health through its influences on the
processes occurring between systems (e.g., practitioner presumptions of heterosexuality;
Utamsingh, Richman, Martin, Lattanner, & Chaikind, 2015), between people (e.g., engaging in
safe sex behaviors; Baptiste-Roberts, Oranuba, Werts, & Edwards, 2017) and/or internally (e.g.,
feelings of sexual communication self-efficacy; Meyer, 2003; Quinn-Nilas, et al., 2016). For
example, sexuality education often takes a heteronormative perspective and excludes important
and affirming information for queer individuals about sexual health, which leaves queer
individuals at higher risk for health disparities (Baptiste-Roberts, et al., 2017). Additionally,
cultural heteronormative scripts suggest that women should be sexually ambivalent whereas men
should be sexually aggressive, contributing to a gendered power dynamic where women’s needs
are second to men’s in heterosexual sexual encounters (Currier, 2013). Often, these
heteronormative structures and scripts create challenges for queer individuals and women to
advocate for their sexual health and limits their knowledge of how to engage in processes that
may benefit sexual health outcomes (such as using barrier methods in sexual intercourse;
Marazzo, Coffey, & Bingham, 2005; Lehmiller, VanderDrift, & Kelly, 2014; Quinn-Nilas et al.,
2016).

Statement of Purpose
The first aim of the program of research is to create a more comprehensive understanding
of sexual health disparities. Current research has taken a disease-centered approach to sexual
health, which only provides a restricted understanding of sexual health disparities (ODPHP,
2019; Zielinski, 2013). Importantly, there is evidence that sexual health disparities span more
than just the absence of disease and unintended pregnancy, but these indicators are understudied
(e.g., Allyn, 2000; Human Rights Campaign, 2019; Kinsey Institute, 2019; Zielinski, 2013). By
employing a comprehensive definition of sexual health and expanding sexual health
measurement to more than just disease and unintended pregnancy (i.e., sexual functioning,
sexual pleasure, safety, depression, anxiety, and perceptions of sexual health), we may gain more
comprehensive insight into health disparities.
The second aim of this program of research is to examine heteronormativity’s indirect
influence on systematic, interpersonal, and individual sexual health processes that may
contribute to disparities. Although some research has examined the role that cultural factors,
such as heteronormativity, have on health (e.g., Baptiste-Roberts, et al., 2017; Meyer, 2003), to
our knowledge, no research has examined how heteronormativity acts as a moderating influence
on sexual health disparities in vulnerable populations. Due to their particularly vulnerable
intersections, we focus specifically on queer women (in this program of research-- LGB+) and
heterosexual women. Understanding how culture indirectly influences sexual health disparities
through interpersonal processes may be a step toward creating more equitable sexual health
outcomes for queer and heterosexual women (ODPHP, 2019). Therefore, the purpose of this
program of research is to model how heteronormativity influences interpersonal and individual
processes which may contribute to sexual health disparities across women.
This program of research was split into three manuscripts. The first manuscript created
and validated a comprehensive measure of sexual health using a multi-group confirmatory factor
analysis (CFA). This latent measurement was then utilized in manuscript two and three. The

second manuscript examined how heteronormativity influenced sexual communication
selfefficacy and safe sex behaviors in queer women and how those contributed to comprehensive
sexual health outcomes. Similarly, the third manuscript examined sexual health communication
self-efficacy, safe sex behaviors, and comprehensive sexual health outcomes in heterosexual
women. Together, these manuscripts examined how individual, interpersonal, and cultural
processes interact and contribute to sexual health disparities. Of note, I used the term queer as an
umbrella term to refer to women who are attracted to other women regardless of their
selfidentified sexual orientation (e.g., bisexual, lesbian, pansexual). Because sexual orientation is
comprised of attraction, behavior, and identity, and these may not always align (Vrangalova &
Savin-Williams, 2012), the use of queer is a more inclusive approach to capturing a range of
queerness among women. Each manuscript is outlined below.
Manuscript 1: Creating a Comprehensive Measure of Sexual Health
As stated previously, to date, much of the sexual health research has focused narrowly on
the absence of disease and unintended pregnancy (i.e., physical domains of sexual health).
However, the World Health Organization (WHO; 2019) defines comprehensive sexual health as
well-being across physical, mental, and social domains. Few studies have attempted to create a
comprehensive measure of sexual health and incorporate it into their research. Therefore, most of
the sexual health information we know is about disease and unintended pregnancy (Zielinski,
2013). This perpetuates a narrow perspective of what it means to be sexually healthy, who is
sexually healthy, and processes that contribute to comprehensive sexual health.
When sexual health is reduced to the absence/presence of negative outcomes it reinforces
a stigmatizing and reductionist perspective of sexual health (WHO, 2010a). When positive and
comprehensive indicators of sexual health (such as categorizing orgasm as being sexually
healthy) are included, we promote positive rhetoric and this has potential to slowly change
stigmatizing cultural messages (Ott, Millstein, Ofner, & Halpern-Felsher, 2006). Further, by
expanding the conceptualization of sexual health, it creates the ability to ask new and innovative

questions that a reductionist conceptualization would overlook. These questions may be more
culturally relevant, inclusive, and comprehensive. For example, by including indicators of what
it means to be mentally sexually healthy (i.e., positive perceptions about one’s sexual identity,
low levels of sexual anxiety) we can ask questions about how cultural discrimination of some
groups, such as sexual minorities, may contribute to the sexual health disparities these groups
face (Hatzenbuehler, 2010).
Thus, the purpose of this study was to create and validate a comprehensive measure of
sexual health through a multi-group confirmatory factor analysis. As informed by the WHO’s
(2019) definition of sexual health, this measure included indicators of anxiety, depression,
perceived physical sexual health, safety, sexual functioning, sexual satisfaction and pleasure, and
STIs/HIV. Once validated, this measure was used in manuscripts two and three.
Manuscript 2: The Impact of Heteronormativity on Queer Women’s Communication
Processes and Comprehensive Sexual Health
For queer individuals, heteronormative sexual scripts are often negative (e.g.,
homophobic; Meyer, 2003) or simply lacking information important for these groups (i.e.
noninclusive sex education; Baptiste-Roberts, et al., 2017). For example, many queer individuals
report never having learned about sex outside of heterosexual relationships throughout their
sexuality education (Baptiste-Roberts et al., 2017). GLSEN (2015) states that omitting queer
sexual health information in sexuality education puts queer individuals at greater risk for
negative sexual health outcomes. Further, queer women are often perceived to be at less risk for
STIs and unintended pregnancy (Baptiste-Roberts, et al., 2017; Power, McNair & Carr, 2009),
and therefore, sexual heath programming frequently ignores them (Baptiste-Roberts, et al.,
2017). Thus, many queer women are unaware of their sexual risk, and report under-using safe
sex practices, such as barrier methods (Baptiste-Roberts, et al., 2017).
Thus, heteronormativity indirectly influences queer women’s engagement in safe sex
behaviors due to inaccurate risk perceptions. Importantly, sexual health communication has been

found to improve sexual health outcomes (Planned Parenthood, 2019; Quinn-Nilas et al., 2016),
and therefore, may be an individual mechanism through which queer women’s sexual health can
be improved. Taken together, the purpose of this study was to model how sexual health
communication self-efficacy can promote more safe-sex behaviors among queer women, and
ultimately lead to better comprehensive sexual health outcomes.
Manuscript 3: Heteronormativity, Sexual Health Communication, and Comprehensive
Sexual Health in Heterosexual Women
For heterosexual men and women, gender socialization often perpetuates power
dynamics (i.e., that men grow up to be strong and aggressive, and women grow up to be quiet
and submissive; Lefkowitz, Shearer, Gillen & Espinosa-Hernandez, 2014; Masters, Casey, Wells,
& Morrison, 2013). Specifically, heterosexual scripts promote hypermasculinity among men
(Ward, 2005) and femininity among women (D’Emilio & Freedman, 2012).
Hypermasculinity is defined as those masculine scripts that promote dominance, hypersexuality,
assume men always want to have sex, and that men are sexually skilled (Masters et al., 2013;
Ward, 2005). Femininity is characterized as not desiring sex, not knowing very much about sex,
and perpetuates higher cultural value of women who have less sexual experience (Masters et al.,
2013). These heterosexual scripts directly promote power imbalances when it comes to sex and
sexual decision making (Rinaldi-Miles, Quick, & LaVoie, 2014). With that, research suggests
that safe sex behaviors are often under-utilized in heterosexual sexual encounters because
women are more likely to follow male condom use preferences (i.e., men report often disliking
the use of condoms; Cook-Lindsay, 2013) and less likely to discuss their safe sex preferences
(Rinaldi-Miles, et al., 2014). Because feminine scripts suggest that women should not
understand their sexuality and should be sexually inexperienced, this promotes silence about
sexuality leading to less communication. Therefore, heteronormativity influences sexual
communication processes, thereby indirectly contributing to health disparities in heterosexual
women. Taken together, the purpose of this study was to examine how heteronormativity

influences sexual health communication, safe-sex behaviors, and comprehensive sexual health
outcomes in heterosexual women
References
Advocates for Youth. (n.d.). Adolescent sexual health in Europe and the United States: A Case
for a Rights. Respect. Responsibility. Approach. Retrieved on May 31, 2019 from
https://www.advocatesforyouth.org/wpcontent/uploads/storage//advfy/documents/adolesc
ent_sexual_health_in_europe_and_the
_united_states.pdf
Allyn, D. (2000). Make love, not war. The sexual revolution: An unfetted history. New York,
United States: Little, Brown and Company.
ASHA. (2019). Statistics. Retrieved on May 12, 2019 from
http://www.ashasexualhealth.org/stdsstis/statistics/
Baptiste-Roberts, K., Oranuba, E., Werts, N., & Edwards, L. V. (2017). Addressing healthcare
disparities among sexual minorities. Obstetrics and Gynecology Clinics of North
America, 44, 71-80. doi: 10.1016/j.ogc.2016.11.003
CDC. (2011). 10 ways STDs impact women differently from men. CDC Fact Sheet. Retrieved
on May 23, 2019 from https://www.cdc.gov/std/health-disparities/STDs-Women-
042011.pdf
CDC. (2015). Special populations. 2015 Sexually Transmitted Diseases Treatment Guidelines.
Retrieved May 29. 2019 from https://www.cdc.gov/std/tg2015/specialpops.htm#WSW
CDC. (2017). STD health equity. Sexually Transmitted Diseases (STDs). Retrieved on May 12,
2019 from https://www.cdc.gov/std/health-disparities/default.htm
CDC. (2018). Chlamydia. Sexually Transmitted Disease Surveillance, 2017. Retrieved on May
11, 2019 from https://www.cdc.gov/std/stats17/chlamydia.htm
Cook-Lindsay, B. A. (2013). Gender-based power imbalances and condom-use negotiations. The
Health Education Monograph Series, 30(2), 28-33. doi: 10.1177/0017896912450240

Currier, D. M. (2013). Strategic ambiguity: Protecting emphasized femininity and hegemonic
masculinity in the hookup culture. Gender & Society, 27(5), 704-727. doi:
10.1177/0891243213493960
D’Emilio, J. D., & Freedman, E. B. (2012). Intimate matters: A history of sexuality. (3ed).
Chicago, United States: The University of Chicago Press.
Easton, D., & Hardy, J. W. (2009). The ethical slut. A practical guide to polyamory, open
relationships, and other adventures (2 ed). Berkeley, CA: Celestial Arts.
ECDC. (2016). Sexually transmitted infections- presentation on annual epidemiological reports
for 2016. Retrieved on June 11, 2019 from
https://ecdc.europa.eu/en/publicationsdata/sexually-transmitted-infections-presentation-
annual-epidemiological-reports-2016
Garcia, J. R., Reiber, C., Massey, S. G., & Merriwether, A. M. (2012). Sexual hook-up culture:
A review. Review of General Psychology, 16(2), 161-176. doi: 10.1037/a0027911
GLSEN. (2015). GLSEN calls for LGBTQ-Inclusive sex ed. Retrieved on May 29, 2019 from
https://www.glsen.org/article/lack-comprehensive-sex-education-putting-lgbtq-youthrisk-
national-organizations-issue-call
Guttmacher Institute. (2019). Unintended pregnancy in the United States. Fact Sheet. Retrieved
on May 12, 2019 from https://www.guttmacher.org/fact-sheet/unintended-
pregnancyunited-states
Hatzenbuehler, M. L. (2010). Social factors as determinants of mental health disparities in LGB
populations: Implications for public policy. Journal of Social Issues & Policy Review, 4,
31-62. doi: 10.1111/j.1751-2409.2010.01017.x
Human Rights Campaign. (2019). Sexual assault and the LGBTQ community. Retrieved on
April 3, 2019 from https://www.hrc.org/resources/sexual-assault-and-the-lgbt-community
Kinsey Institute. (2019). FAQs & sex information. Retrieved on May 29, 2019 from
https://kinseyinstitute.org/research/faq.php

Lefkowitz, E. S., Shearer, C. L., Gillen, M. M., & Espinosa-Hernandez, G. (2014). How
gendered attitudes relate to women’s and men’s sexual behaviors and beliefs. Sexuality
and Culture, 18(4), 833-846. doi: 10.1007/s12119-014-9225-6
Lehmiller, J. J., VanderDrift, L. E., & Kelly, J. R. (2014). Sexual communication, satisfaction,
and condom use behavior in friends with benefits and romantic partners. Journal of Sex
Research, 51, 74-85. doi: 10.1080/00224499.2012.719167
Marazzo, J. M., Coffey, P., & Bingham, A. (2005). Sexual practices, risk perception and
knowledge of sexually transmitted disease risk among lesbian and bisexual women.
Perspectives of Sexual and Reproductive health, 31, 6-12. doi: 10.1363/psrh.37.006.05
Masters, N. T., Casey, E., Wells, E. A., & Morrison, D. M. (2013). Sexual scripts among young
heterosexually active men and women: Continuity and change. Journal of Sex Research,
50(5), 409-420. doi: 10.1080/00224499.2012.661102
Meyer, I. (2003). Prejudice, social stress, and mental health in lesbian, gay, and bisexual
populations: Conceptual issues and research evidence. Psychology of Sexual Orientation
and Gender Diversity, 1(S), 3-26. doi: 10.1037/2329-0382.1.S.3
National LGBT Health Education Center. (2016). Understanding the health needs of LGBT
people. Retrieved on May 23, 2019 from
https://www.lgbthealtheducation.org/wpcontent/uploads/LGBTHealthDisparitiesMar201
6.pdf
ODPHP. (2019). Determinants of Health. Retrieved on April 11, 2019 from
https://www.healthypeople.gov/2020/about/foundation-health-measures/Determinants-of-
Health#individual%20behavior
Ott, M. A., Millstein, S. G., Ofner, S., & Halpern-Felsher, B. L. (2006). Greater expectations:
Adolescents’ positive motivations for sex. Perspectives on Sexual and Reproductive
Health, 38(2), 84-89. doi: 10.1363/3808406

Planned Parenthood. (2019). Tips for Talking. Retrieved on May 20, 2019 from
https://www.plannedparenthood.org/learn/parents/tips-talking
Power, J., McNair, R., & Carr, S. (2009). Absent sexual scripts: Lesbian and bisexual women’s
knowledge, attitudes and action regarding safer sex and sexual health information.
Culture, Health & Sexuality, 11, 67-81. doi: 10.1080/1369105080254167 Quinn-Nilas,
C., Milhausen, R. R., Breuer, R., Bailey, J., Pavlou, M., DiClemente, R. J., &
Wingood, G. M. (2016). Validation of the sexual communication self-efficacy scale.
Health Education and Behavior, 43(2), 165-171. doi: 10.1177/1090198115598986
Ratcliff, K. S. (2017). Social determinants of health. The Social Determinants of Health:
Looking
Upstream (pp. 6-24). Cambridge, UK: Polity.
Rinaldi-Miles, A., Quick, B. L., & LaVoie, N. R. (2014). An examination of the principles of
influence on condom use decision making during casual sex encounters. Health
Communication, 19, 531-541. doi: 10.1080/10410236.2013.765295
Utamsingh, P. D., Richman, L. S., Martin, J. L., Lattanner, M. R., & Chaikind, J. R. (2015).
Heteronormativity and practitioner-patient interaction. Health Communication, 31(5),
566-574. doi: 10.1080/10410236.2014.979975
van Eeden-Moorefield, B. (2018). Introduction to the special issue: Intersectional variations in
the experiences of queer families. Family Relations, 67, 7-11. doi: 10.1111/fare.12305
Vrangalova, Z., & Savin-Williams, R. C. (2012). Mostly heterosexual and mostly gay/lesbian:
Evidence for new sexual orientation identities. Archives of Sexual Behavior, 41, 85-101
doi: 10.1007/s10508-012-9921-y
Ward, E. G. (2005). Homophobia, hypermasculinity and the US black church. Culture, Health &
Sexuality, 7(5), 493-504. doi: 10.1080/13691050500151248
WHO. (2010a). Measuring sexual health: Conceptual and practical considerations related to
indicators. World Health Organization. http://apps.who.int/iris/handle/10665/70434

WHO. (2010b). Social determinants of sexual and reproductive health: Informing future research
and programme implementation. Retrieved on May 16, 2019 from
https://apps.who.int/iris/bitstream/handle/10665/44344/9789241599528_eng.pdf?sequenc
e=1
WHO. (2019). Sexual health. Retrieved on May 29, 2019 from
https://www.who.int/topics/sexual_health/en/
Zielinski, R. (2013). Assessment of women’s sexual health using a holistic, patient centered
approach. Journal of Midwifery and Women’s Health, 58(3), 321-327. doi:
10.1111/jmwh.12044
CHAPTER 2: CREATING A COMPREHENSIVE MEASURE OF SEXUAL HEALTH
Human sexuality is shaped and understood through a series of individual behaviors,
interpersonal exchanges, and social constructions-- biology, mental health, and social exchanges
all contribute to human sexuality and sexual experiences (WHO, 2010). In other words, human
sexuality is more than simply sexual behavior-- it encompasses an entire person interacting with
others in context. Therefore, it makes sense that in order to best understand sexual health we
must conceptualize (and measure) it comprehensively. The World Health Organization (WHO;
2019) defines comprehensive sexual health as the level of well-being across physical, mental,
and social domains. They suggest that comprehensive sexual health “requires a positive and
respectful approach to sexuality and sexual relationships, as well as the possibility of having
pleasurable and safe sexual experiences, free of coercion, discrimination, and violence” (WHO,
2019, p.1). Many of the leading national organizations consider this the standard when defining
sexual health (ASHA, 2020; CDC, 2020; WHO, 2019). However, to date, much of the extant
literature has focused primarily on only the physical domain, more generally, and on the
presence/absence of disease (e.g., Everett, 2013; Weitzman et al., 2019) and unintended
pregnancy (e.g., Finer & Zolna, 2011; Madden et al., 2019), more specifically.

From this limited view focused on physical sexual health, we know that significant health
disparities exist across various parts of the population and particularly among women. For
example, women are more likely than men to contract and experience complications from a
sexually transmitted infection (STI; CDC, 2019). Additionally, in 2011, there were 2.8 million
unintended pregnancies among women in the United States with significant variations among
women based on various intersectional social locations (Guttmacher Institute, 2019). Rates were
highest among low-income women, women between the ages of 18 and 24, women who
cohabited with a partner, and women of color, compared to those who had higher income, were
White, had graduated college, and were married respectively (Guttmacher, 2019). Across these
population based studies, it is clear that disparities exist across different groups of women.
Only recently have studies started to consider and examine the sexual health of queer
women (i.e., an umbrella term for lesbian, bisexual, pansexual, and women who have sex with
other women). This emergent research suggests that cisgender queer women are less likely to use
protective barriers when engaging in same-gender sexual behavior, putting them at greater risk
for STI transmission. For example, rates of Human Papilloma Virus (HPV) and Herpes Simplex
Virus 2 (HSV2) are particularly high in cisgender queer female populations (e.g., 36% of women
who reported a same gender partner in their lifetime have HSV 2; CDC, 2015). It is also
important to acknowledge that these disparities are even higher among trans* women, regardless
of their sexual orientation (CDC, 2019)
Thus, there appears to be a disconnect between leading definitions of sexual health and
the conceptualizations and measurement strategies of sexual health used in the extant literature.
Importantly, the definition of a construct informs the conceptualization of a construct, which then
informs the later measurement of that construct (Engel & Schutt, 2014). Additionally, when
constructing surveys, it is critical to consider best practices for survey length, time to
completion, and funding, to ensure adequate response rates (Urban & van Eeden-Moorefield,
2018), which may dissuade researchers from attempting to measure complex and comprehensive

constructs. Constructs, such as comprehensive sexual health, may be complex and therefore, it is
critical to include all of the dimensions within conceptualizations to ensure accurate yet,
parsimonious measurement (Engel & Schutt, 2014).
Therefore, the purpose of this study was to create and validate (e.g., construct validity;
Urban & van Eeden-Moorefield, 2018) a comprehensive measure of sexual health for women
that has the potential to add to surveys without overburdening participants by adding too much
length or time (See Figure 2.1). The model was grounded in WHO’s (2019) conceptual
framework of comprehensive sexual health, using a multi-group confirmatory factor analysis
(CFA). Informed by the extant literature, the indicator variables included to ensure the presence
of each of the three domains were: anxiety, depression, perceived sexual health, feelings of
safety, sexual functioning, sexual satisfaction/pleasure, and STIs/HIV. Given the between group
sexual health disparities present among queer and heterosexual women, a multi-group CFA was
conducted to ensure model fit for both groups.
Literature Review
Again, the WHO (2019) defines comprehensive sexual health as “requir[ing] a positive
and respectful approach to sexuality and sexual relationships, as well as the possibility of having
pleasurable and safe sexual experiences, free of coercion, discrimination, and violence” (p.1).
Using this definition and the extant literature, the author identified seven observed variables to
create a latent measure of comprehensive sexual health: anxiety, depression, perceived sexual
health, feelings of safety, sexual functioning, sexual satisfaction/pleasure, and STIs/HIV. All of
these indicators fall under one of the domains of sexual health (i.e., physical, mental, social).
These indicators have all been studied in the sexuality-related literature and therefore, should
work together to measure comprehensive sexual health. These are outlined below.
Physical Domain
Sexual Functioning. Sexual functioning has been widely examined across the extant
sexual health literature (e.g., Stefanou & McCabe, 2012) and has been used as a significant

indicator of sexual health (WHO, 2010). Sexual functioning (and/or sexual dysfunction) has
most often been studied in the context of aging (e.g., Clayton & Harsh, 2016), illness (e.g.,
Boquiren et al., 2016 ), and/or trauma (e.g., DiMauro, Renshaw, & Blais, 2018). For example,
Clayton and Harsh (2016) examined sexual functioning across aging. They stated that across the
life course, women experience multiple biological, mental, and social factors that may impact
their sexual functioning. Specifically, female bodies change due to hormone shifts, pregnancy
and childbirth, medical problems and medication, as well as mental health issues such as
depression. Similarly, WHO (2010), states that sexual functioning is strongly linked to
psychological and social processes that are beyond the scope of the person. Thus, sexual
functioning is a strong predictor of sexual health across diverse contexts and throughout a
woman’s life, suggesting that it would contribute to the measurement of comprehensive sexual
health.
STI/HIV. STI and HIV diagnoses are a traditional indicator of sexual health. In the extant
literature, the absence of disease is indicative of good sexual health, which has led to many
prevention initiatives across the globe (WHO, 2010). For example, the CDC conducts STI and
HIV population based surveillance studies to examine the prevalence and disparities across
diagnoses (e.g., CDC, 2018). Within the literature, STI and HIV diagnoses have most commonly,
been studied within male populations, and specifically in men who have sex with other men due
to high prevalence rates (Beyrer, et al., 2013). Additionally, much of the extant literature that has
examined women, STIs, and HIV examines experiences of women in other countries (e.g., Dude,
2011). Of those that examine HIV and STI rates of women in the United States, many focus on
minoritized populations. For example, Painter, Wingwood, DiClemente, DePadilla, & Simpson-
Robinson (2012) surveyed 848 African American college women about their educational
attainment and STI/HIV risk. Surveys asked about demographic, psychosocial, and behavioral
indicators and also cross-referenced biological vaginal swabs that tested for STIs. They found
that African American women who attended college were 73% less likely to have an STI or HIV

when compared to those who did not. Taken together, STIs and HIV have been vastly explored
across the literature with diverse populations, and should be a good indicator of sexual health.
Mental Domain
Anxiety. Sexual anxiety is defined as discomfort, worry, or anxiety about one’s self
and/or sexuality (Brassard, Dupuy, Bergeron, & Shaver, 2015). Much of the extant sexual health
research has examined the impact of anxiety on sexual functioning and sexual satisfaction (e.g.,
Brassard et al., 2015). For example, Brassard and colleagues (2015) conducted a mediation
analysis which examined the role that sexual anxiety had in women’s sexual functioning and
satisfaction. They surveyed 556 women who had anxious and avoidant attachment styles and
found that women with higher levels of sexual anxiety, and lower levels of sexual self-esteem,
had lower sexual functioning and lower sexual satisfaction. Research also suggests that anxiety
may contribute differently to sexual health outcomes for queer and heterosexual women. Beaber
and Werner (2009) examined the relationship between anxiety and sexual functioning in lesbian
and heterosexual women using online surveys which targeted women with anxiety. They found
that lesbian women reported more sexual satisfaction than heterosexual women (i.e., higher
levels of arousal and higher frequency of orgasms). Contrastingly, heterosexual women with
anxiety experienced lower levels of sexual functioning and sexual satisfaction. Studies such as
these suggest that sexual anxiety is an indicator of sexual health, which supports that it would be
a strong indicator of comprehensive sexual health.
Depression. Much of the extant literature has examined depression as a contributor to
sexual health outcomes. The research suggests that women are more likely than men to
experience depression, which in turn contributes to greater sexual dysfunction (i.e., lubrication,
desire, orgasm; Dobkin, Leiblum, Rosen, Menza & Marin, 2006). Additionally, many of the
medications used to treat depression reduce women’s sexual interest and sexual response
(Dobkin, 2006). Lykins, Janssen, and Graham (2006) examined how anxiety and depression
contributed to college aged women’s sexual excitation and inhibition. They found that most

women were not interested in engaging in sexual behavior when they were anxious or depressed.
In another study on college women with depression, Frolich and Meston (2002) found that
women who had depression were had lower sexual satisfaction, lower arousal, more inhibited
orgasms, and more sexual pain. Additionally, they found that women who were depressed were
more likely to engage in solo masturbation when compared to their non-depressed counterparts.
However, the use of depression as an indicator of sexual health has been underexplored.
For queer and heterosexual women, heteronormative cultural messages that silence and shame
women for their sexuality may contribute to negative mental health outcomes, such as depression
(Easton & Hardy, 2009). Additionally, for queer individuals, cultural discrimination and
homophobia may lead to depression (Meyer, 2003). Thus, depression may be an indicator of
sexual health and therefore, should be included in the comprehensive measurement of it.
Perceived Sexual Health. Perceived sexual health consists of one’s own perception of
how sexually health they are. In the sexual health research, this self-perception of sexual health
as an indicator of sexual health has been underexplored. Hebernick and colleagues (2010)
examined women’s sexual behaviors, relationships, and perceived health status using the
NSSHB national dataset. They found that women who perceived themselves to be more sexually
healthy were more interested in engaging in sex, may have more opportunities to engage in sex,
and may have an easier time engaging in sexual intercourse. Thus, perceptions may be influential
in a woman’s desire and overall, perception of her sexuality. Therefore, perceptions of sexual
health may be a strong indicator of sexual health.
Social Domain
Sexual Satisfaction. Sexual satisfaction has been largely examined in the previous
literature. Specifically, the extant literature has studied individual, interpersonal, and cultural
factors that contribute to sexual satisfaction (e.g., Biss & Horne, 2005) as well as other relational
processes that sexual satisfaction is related to (e.g., relationship satisfaction; Heiman et al.,
2011). Specifically, sexual satisfaction has been found to be a key contributor to overall

wellbeing across the lifespan for women (Woloski-Wruble, Oliel, Leefsma, & Hochner-
Celnikier, 2010). Holmberg, Blair, and Phillips (2010), modeled how sexual satisfaction related
to relationship well-being, mental health, and physical health for women in same-gender vs.
mixedgender relationships. They found that sexual satisfaction was a strong predictor of
relationship well-being and mental health regardless of relationship type. Additionally, sexual
satisfaction may be a sexual health outcome that is influenced by mental health and culture (Biss
& Horne, 2005). Biss and Horne (2005) surveyed 596 queer men and women to understand how
psychological well-being, in the context of a heteronormative culture, influenced sexual
satisfaction. They found that living with a partner, age, internalized homonegativity, and other
relational processes all contributed to sexual satisfaction. Therefore, sexual satisfaction may be
an indicator of comprehensive sexual health and therefore, was included in the model.
Safety. Outside of the sexual assault literature (e.g., Ahrens, Abeling, Ahmad, &
Hinman, 2010), scant sexual health research has examined the role that feeling safe in a sexual
encounter has on women’s sexual health outcomes. Additionally, most of the sexual health
research that examines safety in sexual encounters focuses on safe sex behaviors (e.g., McBride,
& Fortenberry, 2010), rather than feeling safe in the sexual encounters. In other words, this
indicator has been underexplored as an indicator of sexual health in the context of consensual
relationships. However according to the WHO (2019) definition of sexual health, feeling safe is
an important aspect. Thus, theoretically, feelings of safety during a sexual encounter should be a
strong indicator of sexual health, and therefore, it was added to the model.
Summary
In summary, these seven indicators have been used, to some extent, as indicators of
sexual health across the extant sexual health literature. However, no study has examined how
they function together to measure comprehensive sexual health. Importantly, these indicators are
grounded in the WHO (2019) conceptualization of comprehensive sexual health, suggesting
theoretical support. Specifically, they span all sexual health domains, as defined by WHO

(2019), and have all been used to measure sexual health to some extent. Therefore, it is predicted
that these indicators should accurately and comprehensively measure sexual health as a latent
variable.
Methods
Data Collection
Using social media to recruit participants for research has become popular, due to its
ability to reach widespread diverse networks and its ease of online survey dissemination (Urban
& van Eeden-Moorefield, 2018; Gelinas et al., 2017). Also, online surveys have been found to be
a useful methodology when discussing sensitive information, such as questions about sex and
health, because of their enhanced anonymity (i.e., the researcher may never know the identity of
the participant; Lefever, Dal, & Matthaisdottir, 2007). Accordingly, data were collected using a
30-minute online cross-sectional survey created in Qualtrics. The recruitment announcement
(Appendix A) and survey link were posted on the research team members’ personal Facebook
profiles, which asked friends to participate in a survey about sexual health. The announcement
also asked Facebook friends to please share the recruitment announcement on their own
Facebook pages (i.e., convenience/snowball sampling). Facebook has become a popular forum
for survey recruitment because of its widespread use and ability to reach diverse populations
(Pederson & Kurz, 2016). Additionally, studies focused on health have had particular success
recruiting participants through Facebook because of its low cost and ability to reach participants
for follow up questions if necessary (Pederson & Kurz, 2016). Participants who decided to
participate in the survey, clicked the survey link and were redirected to the Qualtrics survey
(Qualtrics, 2020). At the beginning of the survey, participants were required to provide informed
consent (Appendix B) and could only participate if they were 18 years or older. From there, they
were redirected to the survey questions (Appendix C). At the end of the survey, in the Thank
You message (Appendix D), participants were provided the option to enter a raffle to win one of
40 $25 Amazon gift cards. If participants decided that they wanted to participate, they clicked a

link which redirected them to a separate unlinked survey (Appendix E), which asked for their
email address. All identifying information was kept separate from survey responses to ensure
anonymity of survey responses. Participants were only allowed to participate in the survey one
time to ensure data independence. In other words, the survey could not be completed multiple
times from the same IP address (Birnbaum, 2004).
Participants
The sample consisted of a convenience sample of 247 cisgender heterosexual and queer
women. This met power needs for the analysis (.90; G*Power). Participants’ ages ranged from
19 to 82 years old (M = 33.26, SD = 10.27). The majority of the sample self-identified as
heterosexual (76.10%) followed by women who identified as bisexual (9.70%), lesbian (5.70%),
pansexual (4.0%), queer (2.40%), and asexual (2.0%). The majority of the sample was
NonHispanic White (89.10%) followed by Latina or Hispanic (7.30%), East Asian/Asian
American
(2.0%), Native America/Alaska Native (1.20%), South Asian/Indian American (1.20%), Middle
Eastern/Arab American (1.20%), Black or African American (<1.00%), and Hawaiian or Pacific
Islander (<1.00%). The sample was highly educated: 78.90% of participants reported earning a
Bachelor’s degree or an advanced degree (e.g., Master’s, PhD). Five percent of the sample
earned a high school degree, 9.70% took some college courses, 4.50% earned an Associate’s
degree, and 1.60% of participants reported technical school education. Additionally, more than
half of our participants reported a yearly household income of more than $75,000.
Measures
The survey asked participants general demographic information (e.g., age, sexual
identity, race/ethnicity). Additionally, participants were asked to reflect on their sexual
experiences within the last 12 months when answering all questions. With regard to STI/HIV
diagnoses, the CDC (2015) suggests that individuals get tested every 12 months and therefore,
some sexual health outcomes may not become known until 12 months later. All measurement

scores were coded and summed so that higher scores indicated better comprehensive sexual
health (e.g., lower depression scores indicated better sexual health so they were reversed coded;
See Table 2.1).
Anxiety. A three-item author created scale measured sexual anxiety. A sample question
was “I generally feel anxious about masturbation” (1= Not true of me at all, 7= Very true of me).
This scale was reversed scored so that higher scores indicated lower sexual anxiety.
Depression. A modified 10-item version of Radloff (1977) CESD-R was used to measure
depressive symptoms. Questions asked participants to indicate the number of times they felt or
behaved in a certain way in the last week (1= Rarely or none of the time; less than 1 day, 4=
Most or all of the time; 5-7 days). A sample question included: “I had trouble keeping my mind
on what I was doing.” This scale was reversed scored so that higher scores indicated lower levels
of depression (i.e., more sexual health).
Perceived sexual health. A global perceived sexual health measure was created by the
author(s). The question asked, “To what extent do you feel you are physically healthy enough to
have sex?”(1= Not at all healthy, 4=Very healthy). Most participants believed that they were
physically healthy enough to have sex.
Safety. An author created global measure of perceived safety in sexual encounters was
used. The question asked “Think about the last time you engaged in sex with a partner. How safe
did you feel?” (1= Not safe at all, 5=Very safe). Most participants reported feeling very safe in
their sexual encounters.
Sexual functioning. A modified 5-item version of Rosen’s (2000) Female Sexual
Function Index was used to assess female sexual functioning (e.g., lubrication). A sample
question was “How often did you find it difficult to have an orgasm when you wanted to?” (1=
Never, 7= Always). Scores were reversed coded so that higher scores reflected higher sexual
functioning (in contrast to higher sexual dysfunction).
Sexual Satisfaction. The author modified a version of the Male Sexual Health

Questionnaire (Rosen et al., 2004) to use with women to measure sexual satisfaction.
Specifically, gendered language was removed so that questions were inclusive of women. A
sample question included “How satisfied are you with the quality of the sex life you have?” (1=
Not at all satisfied, 5= Very satisfied).
STIs/HIV. Author created questions were used to assess participant STI and HIV
diagnoses and experiences. Questions asked the number of times participants had been
diagnosed with Chlamydia, Gonorrhea, and/or Syphilis over the last year. Questions also asked if
participants had herpes and/or HIV because they are treatable chronic conditions (i.e., you can
only get them once); two single-item measures were used to identify if participants had herpes or
HIV. The questions asked, “Do you have herpes?” and “Do you have HIV?” Answers included
“yes, no, not sure, prefer not to answer.” In this sample, no women responded that they were
HIV positive and therefore, HIV was excluded from scale combination. Because herpes is a
chronic condition, it can only be contracted once and therefore herpes was recoded so that yes =
1 and no = 0. Then all STI scores were combined. Higher scores indicted fewer STIs and
therefore, better sexual health. Most participants had never been diagnoses with an STI.
Data Analysis Plan
Through substantial research and conceptual grounding in the WHO’s (2019) definition
of sexual health, criteria for model specification were met prior to data analysis. Specifically,
seven factors were identified as important concepts of sexual health and used as indicators to be
loaded onto one latent variable of comprehensive sexual health. No factors or measurement
errors were hypothesized to be correlated to one another initially, but some research indicates
that some correlations might be plausible. This was considered during analysis. Next, model
identification was assessed. This model was over-identified (df=14) and therefore, parameter
estimation occurred.
Data were imported into SPSS for cleaning, assessment of normality, and assessment of
missingness. Responses were missing at random (i.e., no more than 20% missing per variable;

Schumacker & Lomax, 2010). Data were then imported into Mplus 8.0 and missing data were
computed using Full Information Maximum Likelihood (FIML; Muthen & Muthen, 2017)
because of its reliability to produce accurate, unbiased, and robust estimates when compared to
other missing data strategies (e.g., similar response pattern imputation; Enders & Bandalos,
2001). Additionally, FIML is less likely to have convergence failures when running SEM (Enders
& Bandalos, 2001). One heterosexual woman was excluded because data was missing on all
variables making the final sample size 246.
Using Maximum Likelihood Estimation with standardized output, we conducted a
multigroup confirmatory factor analysis (CFA) to assess model fit. Chi Square (χ2) test, Root
Mean
Square Error Approximation (RMSEA), and Critical Fit Index (CFI; Schumacker & Lomax,
2010) were used as model fit indicators. Mplus automatically sets one factor loading to 1.
Additionally, standardized estimates and standard errors were recorded for each observed factor,
which showed the factors that were significant contributors to the latent variable and accounted
for more of the variance across the latent measure. Additionally, MODINDICIES were used to
identify any theoretically sound modifications that could be added to enhance model fit (Muthen
& Muthen, 2017; Schumacker & Lomax, 2010).
Results
A multi-group confirmatory factor analysis (CFA) was conducted using maximum
likelihood estimation (Schumacker & Lomax, 2010) to ensure fit of the measurement model for
both queer and heterosexual women. Originally, model fit was not strong (e.g., RMSEA > .07).
However, modification indices suggested that sexual functioning and safety be correlated and
sexual satisfaction and safety be correlated, for better model fit. These correlations were added to
the model, because theoretically they made sense although there is limited empirical evidence
that has examined these relationships: if a woman feels safe she may experience better sexual
functioning and more sexual satisfaction (Jozkowski & Wiersma- Mosley, 2015). Once these

modifications were added, model fit indices denoted strong fit (RMSEA = 0.06, CFI = 0.93, TLI
= 0.92). However, the chi-square test suggested slight differences in the queer and heterosexual
latent measurement models, particularly regarding strength of factor loadings χ2 (36, N = 246) =
52.89, p < .05. Importantly, all significance of factor loadings remained the same across both
models.
All factor loadings for both models were statistically significant except for STI diagnoses
(see Table 2.2, Figure 2.2, and Figure 2.3). Theoretically, STI diagnoses should be a strong
indicator of sexual health. Therefore, this path was not trimmed from the model. Additionally,
84.60% of participants reported that they had never been diagnosed with an STI, so there was
limited variation across STI diagnoses scores. Sexual satisfaction, anxiety, and sexual
functioning had the strongest factor loadings for both queer and heterosexual women, however
the strength of the factor loadings differed. Specifically, sexual satisfaction, anxiety, and sexual
functioning had a moderate to large effect on queer women’s comprehensive sexual health. In
contrast, these indicators had small to moderate effect on heterosexual women’s comprehensive
sexual health.
Discussion
A multigroup CFA was used to validate the latent measure of comprehensive sexual
health, grounded in the WHO’s (2019) definition of sexual health, for queer and heterosexual
women. Data from 246 women, from an online survey, collected through social media were used
to validate this measure. The sample was mostly White, highly educated, and made over $75,000
annually, and therefore, relatively homogenous and lacking variation.
Results suggested strong model fit for both queer and heterosexual women, proposing
that this latent measure is a good predictor of comprehensive sexual health for women.
Importantly, this measure is one of the first parsimonious measurements of comprehensive
sexual health and should be used in future research. By using this measurement, scholars may be
able to ask research questions that seek to understand comprehensive sexual health rather than

single biological indicators (e.g., STIs). Additionally, future research can ask questions about
individual, interpersonal, and social influences on comprehensive sexual health, which considers
sexuality as more than biology. For example, new sexual health disparities, specific to women,
can be explored such as orgasm gaps (e.g., Frederick, John, Garcia, & Lloyd, 2017) feelings of
safety in consensual sexual encounters (Jozkowski & Wiersma, 2015), and sexuality specific
anxiety and depression (Kalmbach, Kingsberg, & Cielsa, 2014).
Importantly, sexual satisfaction, anxiety, and sexual functioning strongly loaded onto
comprehensive sexual health, and accounted for a significant amount of variance across the
measurement for both queer and heterosexual women. This is an important finding, because
although the significant chi square statistic suggested that sexual orientation may moderate the
strength of indicator relationship (i.e., queer women and heterosexual women have slightly
different models of sexual health), these three indicators were the strongest factor loadings on
comprehensive sexual health for both models. Queer women’s factor loadings were stronger than
heterosexual women’s suggesting a stronger relationship between those three indicators for queer
women. This is in line with previous literature (e.g., Garcia, Llyod, Wallen, & Risher, 2014;
Frederick, John, Garcia, and Lloyd, 2018).
First, research suggests that queer women experience more sexual satisfaction in their
sexual encounters when compared to heterosexual women (Garcia et al., 2014). Using an online
survey, Garcia and colleagues examined orgasm occurrence across sexual orientation and gender.
They found the mean occurrence of orgasm for lesbian women was 74.70% compared to 61.60%
for heterosexual women. However, interestingly in their study they found that the mean orgasm
rates for bisexual women was less than both lesbian and heterosexual women.
Contrastingly, Frederick and colleagues (2018) used a national sample and found that lesbian and
bisexual women were more likely than heterosexual women to report orgasming while engaging
in sexual intercourse. This study posited that perhaps queer women experienced more orgasms
because women in same-gender sexual encounters are more aware of behaviors that would lead

to sexual satisfaction in their partners when compared to different-gender sexual encounters.
Queer women may experience more sexual satisfaction in their relationships, which may
influence how much it impacts their sexual health. That being said, sexual satisfaction was the
most influential indicator of comprehensive sexual health for both queer and heterosexual
women.
Anxiety was another strong predictor of comprehensive sexual health for queer and
heterosexual women. For women specifically, experiences of anxiety may ebb and flow across
the lifespan, due to life stressors, hormonal fluctuations (Hantsoo & Epperson, 2017) and
cultural values and norms (Hofmann & Hinton, 2014). It is important to note that generally,
women are often shamed for their sexuality, regardless of their sexual orientation (Easton &
Hardy, 2009) and internalizing these beliefs may lead to negative physical and mental health
outcomes (Easton & Hardy, 2009). According to sexual scripting theory (Wiederman, 2005),
culture creates gendered and rigid scripts regarding sexuality and sexual processes. These create
guidelines for sexual behaviors that are often internalized. For women, these scripts teach
women that they should not be sexual or discuss sexuality. Therefore, when women are asked
about their sexuality or their sexual behaviors it is possible that provokes feelings of anxiety
(Wiederman, 2005). However, for queer women, within group cultural scripts promote sexual
pleasure and normalize engaging in sexual behavior (e.g., masturbation; Meiller & Hargons,
2019). Thus, heterosexual women may identify more strongly with larger cultural scripts that
stigmatize female sexuality and thus, it may not be as strong of an indicator of comprehensive
sexual health.
Research suggests that sexual functioning, and particularly sexual dysfunction, is a
common concern for women (Faubion & Rullo, 2015). When a woman experiences sexual
dysfunction, she may lose sexual interest, may find it challenging to become aroused, may not be
able to reach orgasm, and may experience pain during sexual intercourse (Faubion & Rullo,

2015). Sexual functioning may also be contingent upon mental and physical health (Nobre &
Pinto-Gouveia, 2006). For example, Nobre & Pinto-Gouveia (2006) examined emotional
responses to regular thoughts that often occur during sexual activity. They found that both men
and women who had less sexual functioning may experience more thoughts of sadness,
disillusion, and fear (i.e., negative thoughts). Flynn, Lin, and Weinfurt (2017) conducted a
crosssectional online survey to examine sexual function and satisfaction across gender and
sexual orientation. They found that lesbian women may experience less vaginal discomfort,
higher lubrication, and easier orgasms when compared to heterosexual women. However,
bisexual women had more vulvar and labial discomfort, and higher anal discomfort when
compared to heterosexual women. There were no differences among women in clitoral
discomfort, or pleasure from orgasms and sexual satisfaction. Thus, sexual functioning is an
important factor in women’s sexual health and may be varied based on numerous factors.
Future Research and Limitations
Taken together, although models were slightly different, model fit for the latent measure
of comprehensive sexual health for both queer and heterosexual women was strong. It is
important to recognize that sexual satisfaction, anxiety, and sexual functioning were three of the
strongest indicators of comprehensive sexual health across women regardless of their sexual
orientation. Additionally, all indicators except for STI diagnoses were significant measures of
comprehensive sexual health. Future models should examine how STIs play a role in
comprehensive sexual health, since the lack of significance in this model was likely due to error
and homogeneous samples. One such way to gain access to participants with diverse STI
diagnoses would be to recruit through STI clinics that serve at risk populations (Carey, Vanable,
Coury-Doniger, & Urban, 2005). Additionally, populations based studies could employ this
measure of comprehensive sexual health, which would greatly contribute to the literature and
also access diverse populations. Further, while this measure is parsimonious, it may be important
for surveys to be shorter, to ensure that participants complete the survey (Urban & van

EedenMoorefield, 2018). Perhaps creating some single item measurements that encompass each
domain of sexual health (i.e., how physically healthy do you feel, how mentally healthy do you
feel, how socially healthy do you feel), would provide a comprehensive approach to measuring
sexual health.
Moreover, this study did not ask about experiences with unintended pregnancy, which is
a traditional indicator of sexual health. The study chose not to include this indicator within the
comprehensive measurement of sexual health because unintended pregnancy is not mentioned
within the WHO (2019) conceptualization. Future research could include unintended pregnancy
as an indicator of comprehensive measurement of sexual health to understand how that may
change the measurement. Finally, future research should use this model in more diverse
populations to understand comprehensive sexual health across diverse intersections. The sample
used in this study was very homogenous (White) and privileged. The extant literature suggests
that women of color, who are less educated, and low income are disproportionately impacted by
sexual health disparities (CDC, 2020, Guttmacher, 2019). To survey more diverse populations
through social media, future research should use targeted advertisements to encourage diverse
groups of women to participate (NIH, 2020). Therefore, applying this measurement to a sample
that resembles those characteristics more closely may exhibit different results. Taken together,
this study is a first step toward finding a comprehensive measurement of sexual health that
reflects the comprehensive definitions commonly used in health organizations.
References
Ahrens, C. E., Abeling, S., Ahmad, S., & Hinman, J. (2010). Spirituality and well-being: The
relationship between religious coping and recovery from sexual assault. Journal of
Interpersonal Violence, 25(7), 1242-1263. doi: 10.1177/0886260509340533
Allison, R., & Risman, B. J. (2014). “It goes hand in hand with the parties”: Race, class, and
residence in college student negotiations of hooking up. Sociological Perspectives, 57,

102-123. doi: 10.1177/0731121413516608
ASHA. (2020). Understanding sexual health. Retrieved on May 12, 2019 from
http://www.ashasexualhealth.org/sexual-health/
Beaber, T. E., & Werner, P. D. (2009). The relationship between anxiety and sexual functioning
in lesbians and heterosexual women. Journal of Homosexuality, 56(5), 639-654. doi:
10.1080/00918360903005303
Beyrer, C., Sullivan, P., Sanchez, J., Baral, S., Collins, C., Wirtz, A. L., ... Mayer, K. (2013).
The increase in global HIV epidemic in MSM. AIDS, 27(17), 2665-2678. doi:
10.1097/01.aids.0000432449.30239.fe
Birnbaum, M. H. (2004). Human research and data collection via the internet. Annual Review of
Psychology, 55, 803-832. doi: 10.1146/annurev.psych.55.090902.141601
Biss, W. J., & Horne, S. G. (2005). Sexual satisfaction as more than a gendered concept: The
roles of psychological well-being and sexual orientation. Journal of Constructivist
Psychology, 18, 25-38. doi: 10.1080/10720530590523044
Boquiren, V. M., Esplen, M. J., Wong, J., Toner, B., Warner, W., & Malik, N. (2016). Sexual
functioning in breast cancer survivors experiencing body image disturbance. Psycho-
Oncology, 25, 66-76. doi: 10.1002/pon.3819
Brassard, A., Dupuy, E., Bergeron, S., & Shaver, P. R. (2015). Attachment insecurities and
women’s sexual function and satisfaction: The mediating roles of sexual self-esteem,
sexual anxiety, and sexual assertiveness. Journal of Sex Research, 52, 110-119. doi:
10.1080/00224499.2013.838744.
Carey, M. P., Vanable, P. A., Senn, T. E., Coury-Doniger, P., & Urban, M. A. (2005). Recruiting
patients from a sexually transmitted disease clinic to sexual risk reduction workshops:
Are monetary incentives necessary. Journal of Public Health Management Practice,
11(6), 516-521. doi: 10.1097/00124784-200511000-00007
CDC. (2015). Which STD tests should I get? Sexually Transmitted Disease (STDs). Retrieved on

April 18, 2020 from https://www.cdc.gov/std/prevention/screeningreccs.htm
CDC. (2018). Sexually Transmitted Disease Surveillance 2018. Retrieved on April 18, 2020
from https://www.cdc.gov/std/stats18/default.htm
CDC. (2019). HIV and transgender people. Retrieved on April 18, 2020 from
https://www.cdc.gov/hiv/group/gender/transgender/index.html
CDC. (2020). Sexual health. Retrieved from https://www.cdc.gov/sexualhealth/Default.html
Clayton, A. H., & Harsh, V. (2016). Sexual function across aging. Current Psychiatry Reports,
18(28). https://doi.org/10.1007/s11920-016-0661-x
DiMauro, J., Renshaw, K. D., & Blais, R. K. (2018). Sexual vs. non-sexual trauma, sexual
satisfaction and function, and mental health in female veterans. Journal of Trauma &
Dissociation, 4, 403-416. doi: 10.1080/15299732.2018.1451975
Dobkin, R. D., Leiblum, S. R., Rosen, R. C., Menza, M., & Marin, H. (2006). Depression and
sexual functioning in minority women: Current status and future directions. Journal of
Sex and Marital Therapy, 32, 23-36. doi: 10.1080/00926230500229251
Downing-Matibag, T. M., & Geisinger, B. (2009). Hooking up and sexual risk taking among
college students: A health belief model perspective. Qualitative Health Research, 19,
1196-1209. doi: 10.1177/1049732309344206
Dude, A. M., (2011). Spousal intimate partner violence is associated with HIV and other STIs
among married Rwandan women. AIDS Behavior, 15, 142-152. doi: 10.1007/s10461-
009-9526-1
Easton, D., & Hardy, J. W. (2009). The ethical slut. A practical guide to polyamory, open
relationships, and other adventures (2 ed). Berkeley, CA: Celestial Arts.
Enders, C. K., & Bandalos, D. L. (2001). The relative performance of full information maximum
likelihood estimations for missing data in structural equation models. Structural Equation
Modeling: A Multidisciplinary Journal, 8(3), 430-457. doi:
10.1207/s15328007sem0803_5

Engel, R. J., & Schutt, R. K. (2014). Conceptualization and measurement. Fundamentals of
Social Work Research (pp. 67-91). SAGE Publications, Inc.
Everett, B. G. (2013). Sexual orientation disparities in sexually transmitted infections:
Examining the intersection between sexual identity and sexual behavior. Archives of
Sexual Behavior, 42(2), 225-236. doi: 10.1007/s10508-012-9902-1
Faubion, S. S., & Rullo, J. E., (2015). Sexual dysfunction in women: A practical approach.
American Family Physician, 92(4), 281-288.
Finer, L. B., & Zolna, M. R. (2011). Unintended pregnancy in the United States: Incidence and
disparities, 2006. Contraception, 84(5), 478-485. doi:
10.1016/j.contraception.2011.07.013
Flynn, K. E., Lin, L., & Weinfurt, K. P. (2017). Sexual function and satisfaction among
heterosexual and sexual minority U.S. adults: A cross-sectional survey. PLoS One, 12(4),
10.1371/journal.pone.0174981
Frederick, D. A., John, H. K. S., Garcia, J. R., & Lloyd, E. A. (2018). Differences in orgasm
frequency among gay, lesbian, bisexual, and heterosexual men and women in a U.S.
national sample. Archives of Sexual Behavior, 47, 273-288. doi: 10.1007/s10508-017-
0939-z
Frolich, P., & Meston, C. (2002). Sexual functioning and self-reported depressive symptoms
among college women. Journal of Sex Research, 39(4), 321-325. doi:
10.1080/00224490209552156
Garcia, J. R., Lloyd, E. A., Wallen, K., Fisher, H. E. (2014). Variation in orgasm occurrence by
sexual orientation in a sample of US singles. Journal of Sexuality Related Medicine,
11(11), 2645-2652. doi: 10.1111/jsm.12669
Gelinas, L., Pierce, R., Cohen, I. G., Lynch, H. F., & Bierer, B. E. (2017). Using social media as
a research recruitment tool: Ethical issues and recommendations. The American Journal
of Bioethics, 17(3), 3-14. doi: 10.1080/15265161.2016.1276644

Guttmacher Institute. (2019). Unintended pregnancy in the United State. Retrieved from
https://www.guttmacher.org/fact-sheet/unintended-pregnancy-united-states
Hantsoo, L., & Erpperson, C. N. (2017). Anxiety disorders among women: a Female lifespan
approach. FOCUS, 15(2), 162-172. doi: 10.1176/appi.focus.20160042
Hebernick, D., Reece, M., Schick, V., Sanders, S. A., Dodge, B., & Fortenberry, J. D. (2010).
Sexual behaviors, relationships, and perceived health status among adult women in the
United States: Results from a national probability sample. The International Journal for
Sexual Medicine, 7(supp 5), 277-290. doi: 10.1111/j.1743-6109.2010.02010.x
Heiman, J. R., Long, J. S., Smith, S. N., Fisher, W. A., Sand, M. S., & Rosen, R. C. (2011).
Sexual satisfaction and relationship happiness in midlife and older couples in five
countries. Archives of Sexual Behavior, 40, 741-753. doi: 10.1007/s10508-010-9703-3
Hofmann, S. G., & Hinton, D. E. (2014). Cross-cultural aspects of anxiety disorders. Current
Psychiatry Report, 16(6), 450. doi: 10.1007/s11920-014-0450-3
Homberg, D., Blair, K. L., & Phillips, M. (2010). Women’s sexual satisfaction as a predictor of
well-being in same-sex verses mixed-sex relationships. Journal of Sex Research, 47, 1-
11. doi: 10.1080/00224490902898710
Jozkowski, K. N., & Wiersma-Mosley, J. (2015). Does drinking alcohol prior to sexual activity
influence college students’ consent? International Journal of Sexual Health, 27(2), 156-
174. doi: 10.1080/19317611.2014.951505
Kalmbach, D. A., Kingsberg, S. A., Ciesla, J. A. (2014). How changes in depression and anxiety
symptoms correspond to variations in female sexual response in a nonclinical sample of
young women: A daily diary study. The Journal of Sex Medicine, 11(12), 2915-2927. doi:
10.1111/jsm.12692
Lefever, S., Dal, M., & Matthiasdottir, A. (2007). Online data collection in academic research:
Advantages and limitations. British Journal of Educational Technology, 38(4), 574-582.
doi:10.1111/j.1467-8535.2006.00638.x

Lykins, A. D., Janssen, E., & Graham, C. A. (2006). The relationship between negative mood
and sexuality in heterosexual college women and men. Journal of Sex Research, 43(2),
136-143. doi: 10.1080/00224490609552308
Madden, T., Paul, R., Maddipati, R., Buckel, C., Goodman, M., & Peipert, J. F. (2019).
Comparison of unintended pregnancy at 12 months between two contraceptive care
programs; a controlled time-trend design. Contraception, 100(3), 196-201. doi:
10.1016/j.contraception.2019.05.009
McBride, K. R., & Fortenberry, J. D. (2010). Heterosexual anal sexuality and anal sex behaviors:
A review. The Journal of Sex Research, 47(2/3), 123-136. doi:
10.1080/00224490903402538
Meiller, C., & Hargons, C. N. (2019). “It’s happiness and relief and release”: Exploring
masturbation among bisexual and queer women. Journal of Counseling Sexology &
Sexual Wellness: Research, Practice, and Education, 1. https://doi.org/10.34296/
01011009
Meyer, I. (2003). Prejudice, social stress, and mental health in lesbian, gay, and bisexual
populations: Conceptual issues and research evidence. Psychology of Sexual Orientation
and Gender Diversity, 1(S), 3-26. doi: 10.1037/2329-0382.1.S.3
Muthén, L. K, & Muthén, B. O. (1998-2017). Mplus User’s Guide. Eighth Edition. Los Angeles,
CA: Muthén & Muthén
NIH. (2020). NIH inclusion outreach toolkit: How to engage, recruit, and retain women in
clinical research. Retrieved on April 19, 2020 from
https://orwh.od.nih.gov/toolkit/recruitment/cultural-competence
Nobre, P. J., & Pinto- Gouveia, J. (2006). Emotions during sexual activity: Differences between
sexually functional and dysfunctional men and women. Archives of Sexual Behavior, 35,
491-499. doi: 10.1007/s10508-006-9047-1

Painter, J.E., Wingood, G. M., DiClemente, R. J., DePadilla, L. M., & Simpson-Robinison, L.
(2012). College graduation reduces vulnerability to STIs/HIV among African American
young adult women. Women’s Health Issues, 22(3), e303-e310. doi:
10.1016/j.whi.2012.03.001
Pederson, E. R., & Kurz, (2016). Using facebook for health-related research study recruitment
and program delivery. Current Opinion in Psychology, 9, 38-43, doi:
10.1016/j.copsyc.2015.09.011
Qualtrics. (2020). [survey tool]
Radloff, L. S. (1977). The CES-D scale: A self-report depression scale for research in the general
population. Applied Psychological Measurement, 1, 385-401. doi: 10.13072/midss.120
Rosen, R. C., Catania, J., Pollack, L., Althof, S., O’Leary, M., & Seftel, A. D. (2004). Male
sexual health questionnaire (MSHQ): Scale development and psychometric validation.
Adult Urology, 64, 777- 782. doi: 10.1016/j.urology.2004.04.056
Rosen, R., Brown, C., Heiman, J., Leiblum, S., Meston, C., Shabsign, R., ... D’Agostino, R.
(2000). The female sexual function index (FSFI): a multidimensional self-report
instrument for the assessment of female sexual function. Journal of Sexuality and Marital
Therapy, 26(2), 191-208. doi: 10.1080/009262300278597
Schumacker, R. E., & Lomax, R. G. (2010). A beginner’s guide to structural equation modeling
(4th ed). New York, United States: Routledge, Taylor, & Francis Group.
Stefanou, C., & McCabe, M. P. (2012). Adult attachment and sexual functioning: A review of the
past research. The Journal of Sex Medicine, 9(10), 2499-2507. doi: 10.1111/j.1743-
6109.2012.02843.x
Urban, J. B., & van Eeden-Moorefield, B. M. (2018). Designing and proposing your research
project. Washington, DC: American Psychological Association.
Weiderman, M. W. (2005). The gendered nature of sexual scripts. the Family Journal:
Counseling and Therapy for Couples and Families, 13(4), 496-502. doi:

10.1177/1066480705278729
Weitzman, P. F., Zhou, Y., Kogelman, L., Mack, S., Sharir, J. Y., Vicente, S. R...Levkoff, S. E.
(2019). A web-based HIV/STD prevention intervention for divorced or separated older
women. The Gerontologist. doi: 10.1093/geront/gnz098
WHO. (2010). Measuring sexual health: Conceptual and practical consideration and related
indicators. Retrieved from
https://apps.who.int/iris/bitstream/handle/10665/70434/who_rhr_10.12_eng.pdf
WHO. (2019). Sexual health. Retrieved on May 12, 2019 from
https://www.who.int/topics/sexual_health/en/
Woloski-Wruble, A. C., Oliel, Y., Leefsma, M., & Hochner-Celnikier, D. (2010). Sexual
activities, sexual and life satisfaction, and successful aging in women. The Journal of
Sexual Medicine, 7(7), 2401-2410. doi:
10.1111/j.1743-6109.2010.01747.x
Table 2.1
Measurement Descriptive Information
Measure
Min
Max
M (SD)
α
Anx*
3
21
17.49 (4.15)
.70
Dep*
14
40
30.97 (6.35)
.88
PSH
1
4
3.68 (.60)
---
Safe
2
5
4.83 (.53)
---
SFW*
9
35
24.03 (5.73)
.82
SexSat
6
30
21.10 (6.90)
.94
STI*
0
6
5.79 (.80)
.76
Note. *Scales were recoded so that higher scores indicate better sexual health.
Anx= Anxiety, Dep= Depression, PSH= perceived physical sexual health, safe= safety, SFW=
sexual functioning, SexSat= sexual satisfaction, STI= Sexually transmitted infections
Table 2.2
Comprehensive Sexual Health Observed Variable Factor Loadings
Queer Women
Heterosexual Women
Observed Variable
Estimate
S.E.
Observed Variable
Estimate
S.E.
Sexual Satisfaction
0.74*
0.06
Sexual Satisfaction
0.57*
0.06
Anxiety
0.71*
0.07
Anxiety
0.49*
0.06
Sexual Functioning
0.64*
0.07
Sexual Functioning
0.53*
0.07
Depression
0.56*
0.07
Depression
0.50*
0.07
Perceived Sexual
Health
0.51*
0.07
Perceived Sexual
Health
0.41*
0.07
Safety
0.51*
0.07
Safety
0.32*
0.08
STI
0.03
0.08
STI
0.04
0.08
Note. * indicates p<.05
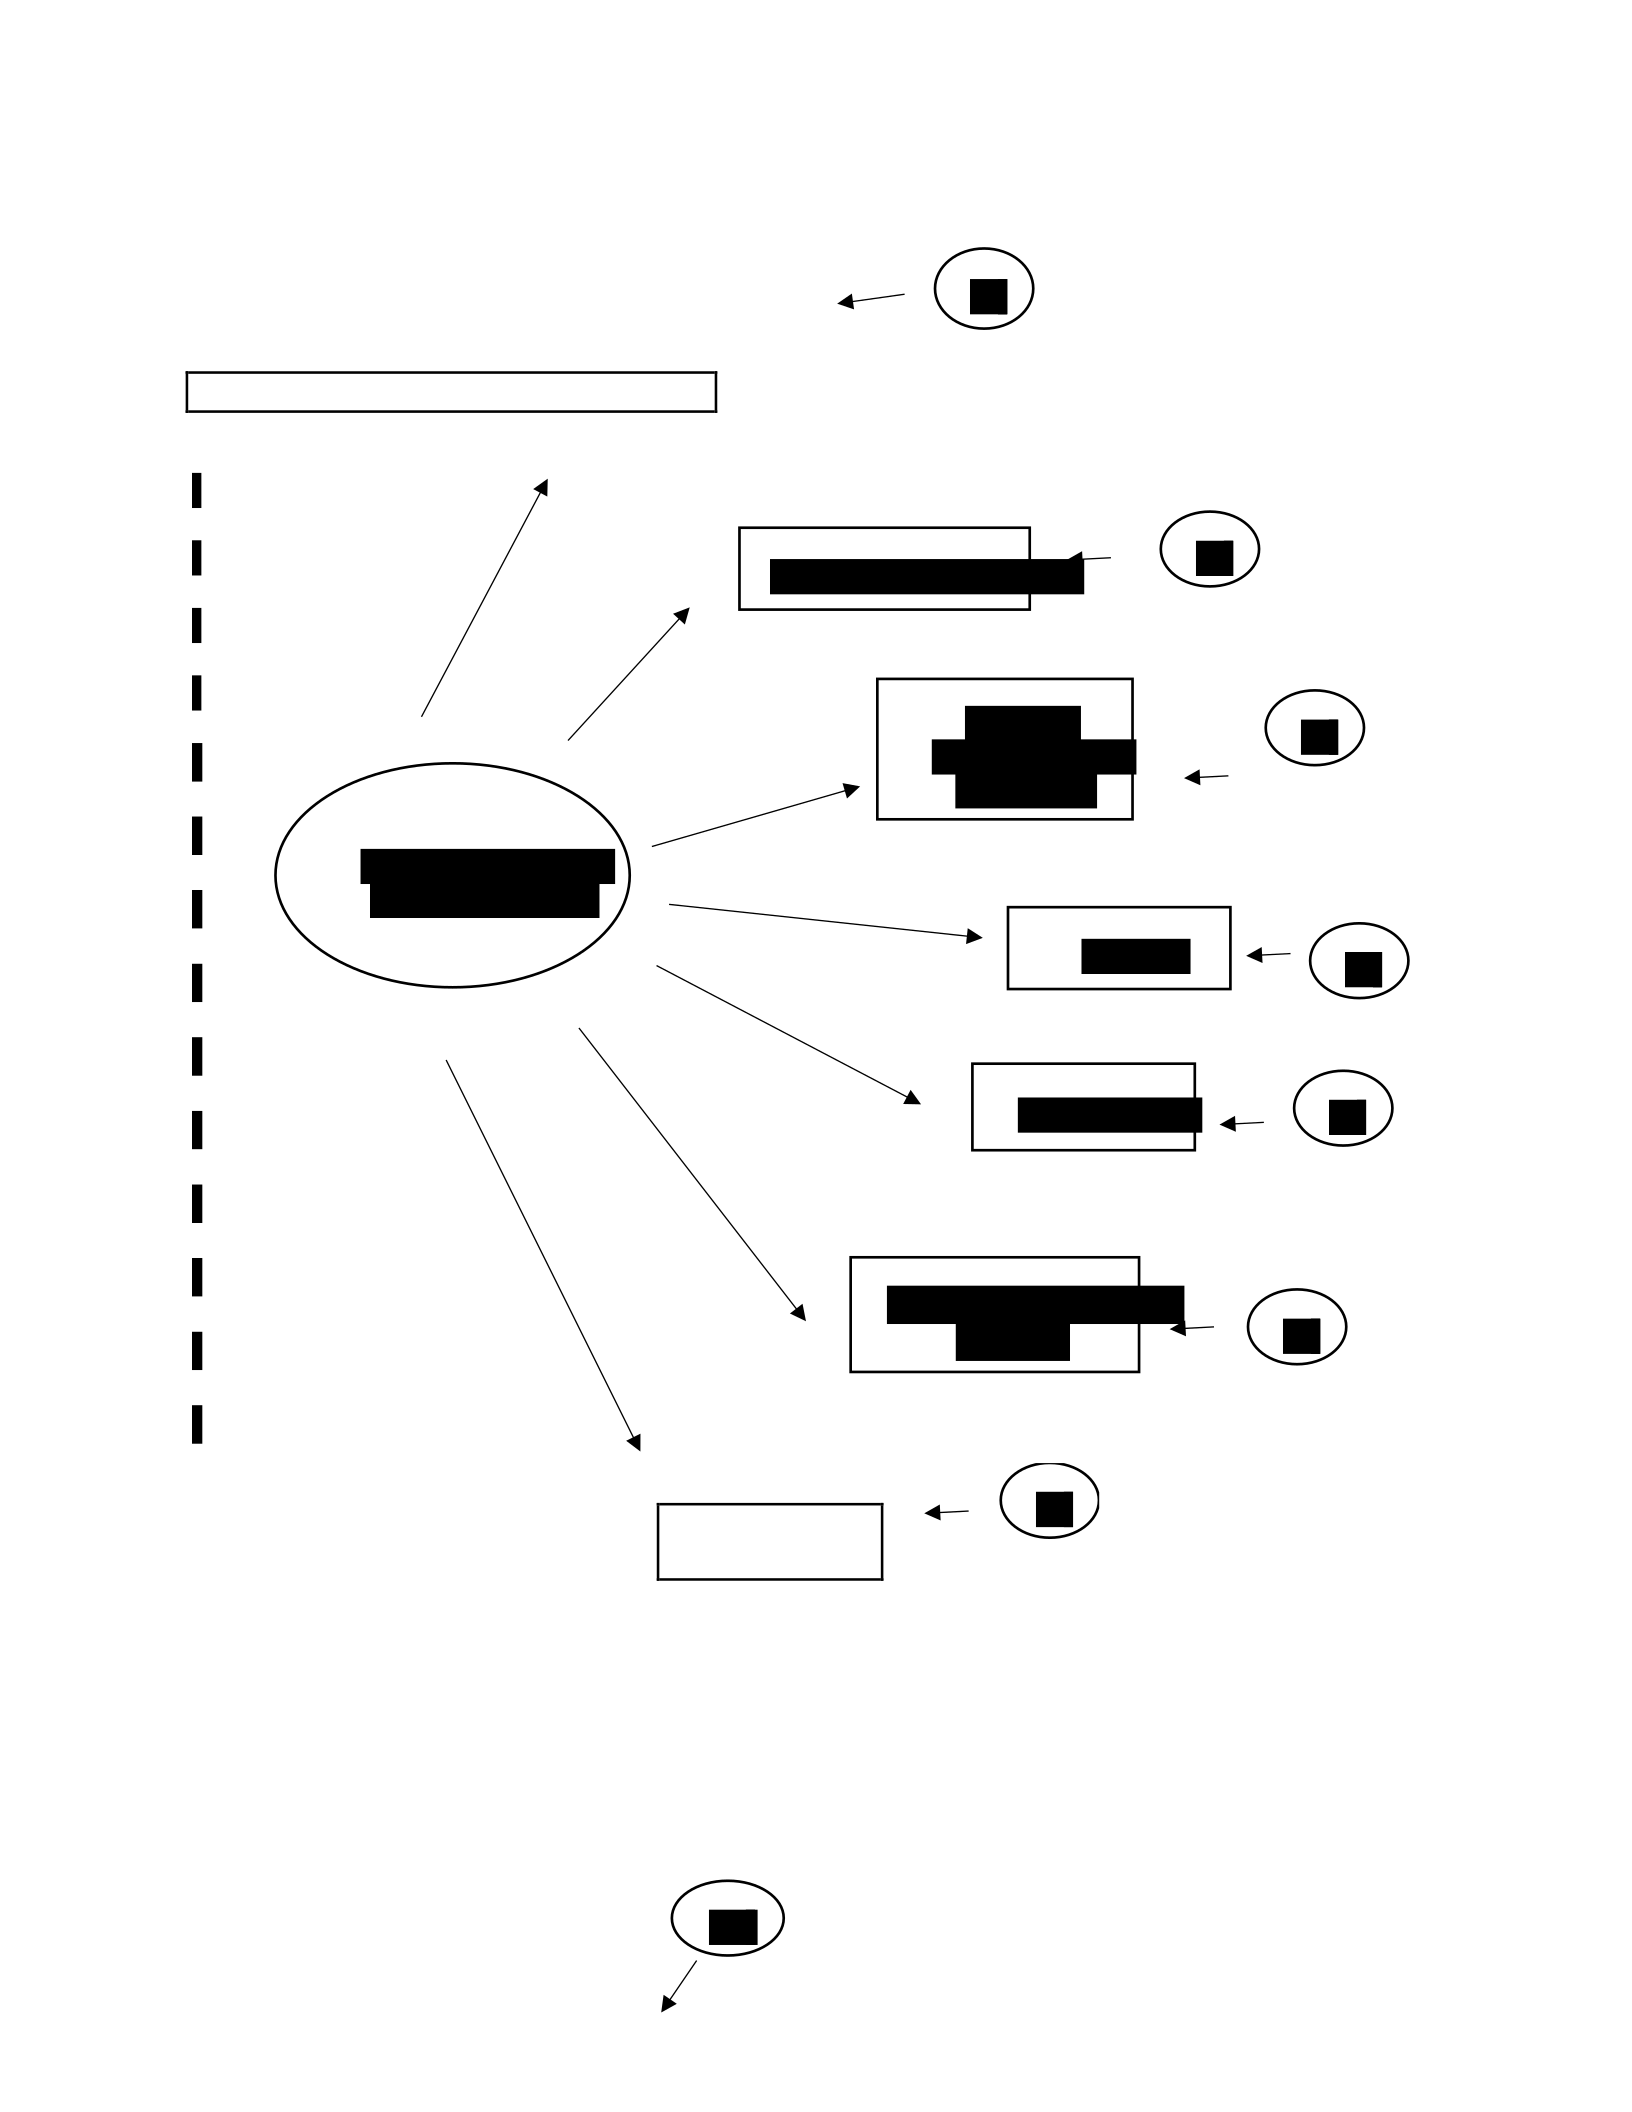
STI/HIV
Anxiety
Figure 2.1. Hypothesized model.
e7
e1
Comprehensive
Sexual Health
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived sexual
health
e2
e3
e4
e5
e6
.08
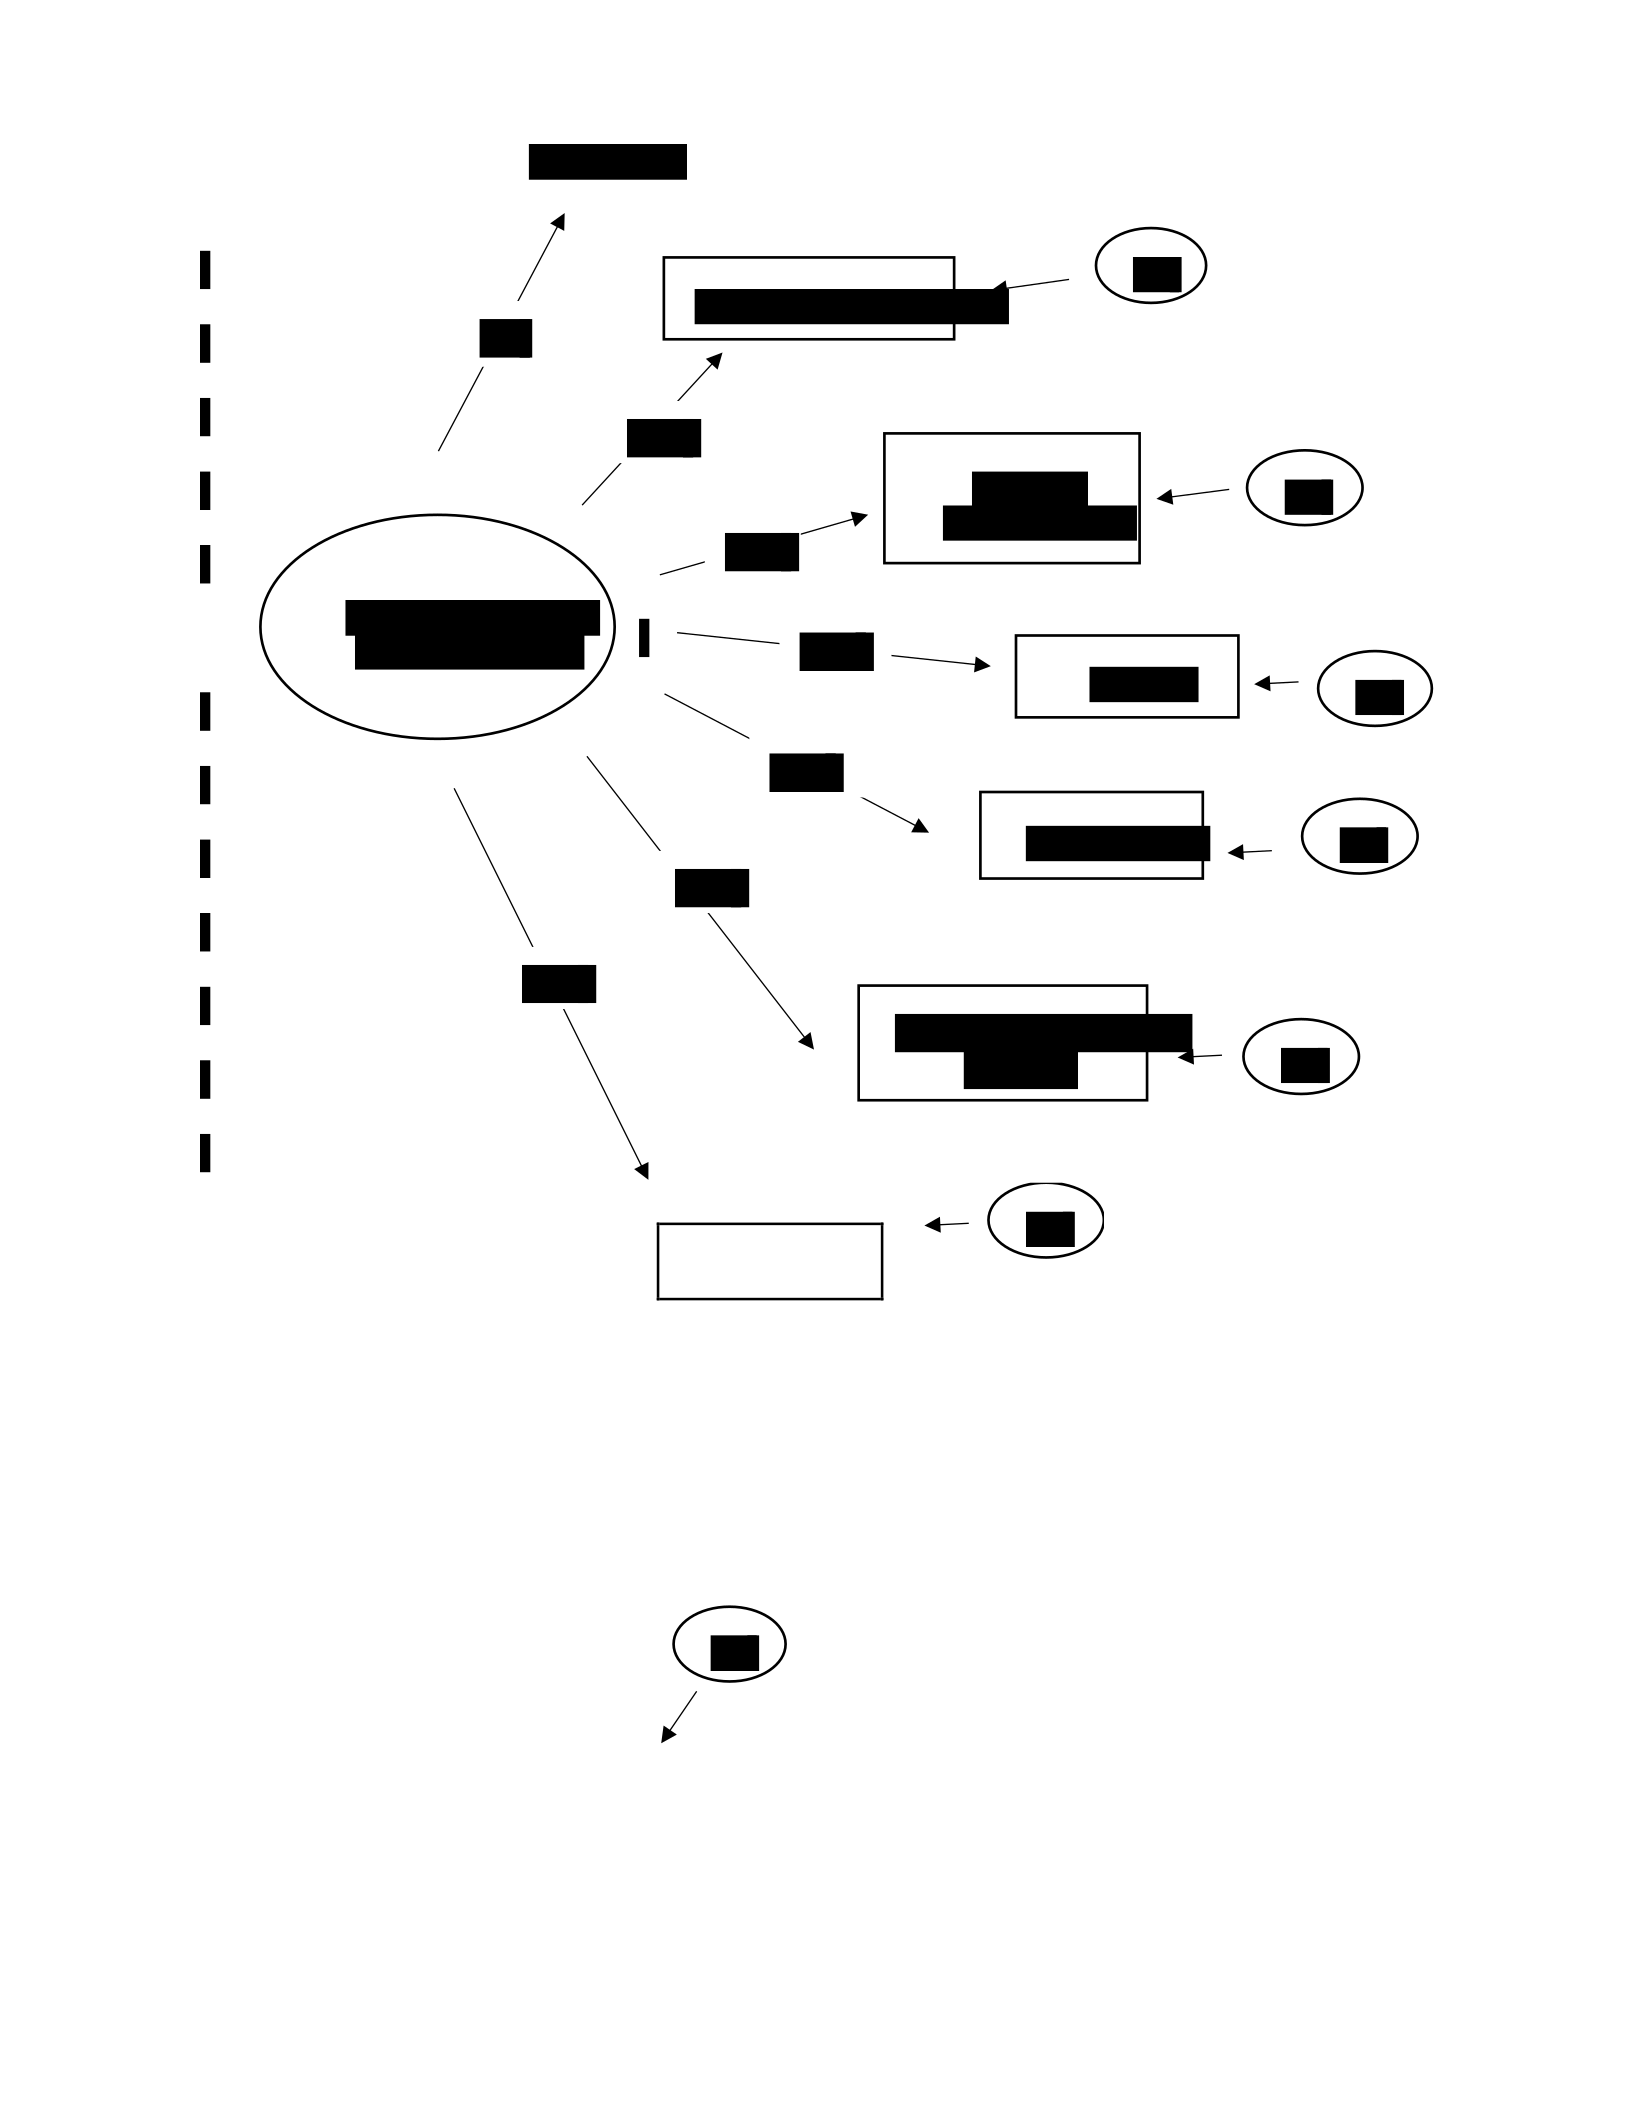
Anxiety
Figure 2.2. Confirmatory factor analysis: seven-factor model of Comprehensive Sexual Health
for queer women with factor loadings and standard error.
Note: * p < .05
.07
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction
Safety
Depression
Perceived sexual
health
.07
.06
.09
.07
.03
.64*
.74*
.40*
.56*
.51*
.07
.71*
.08
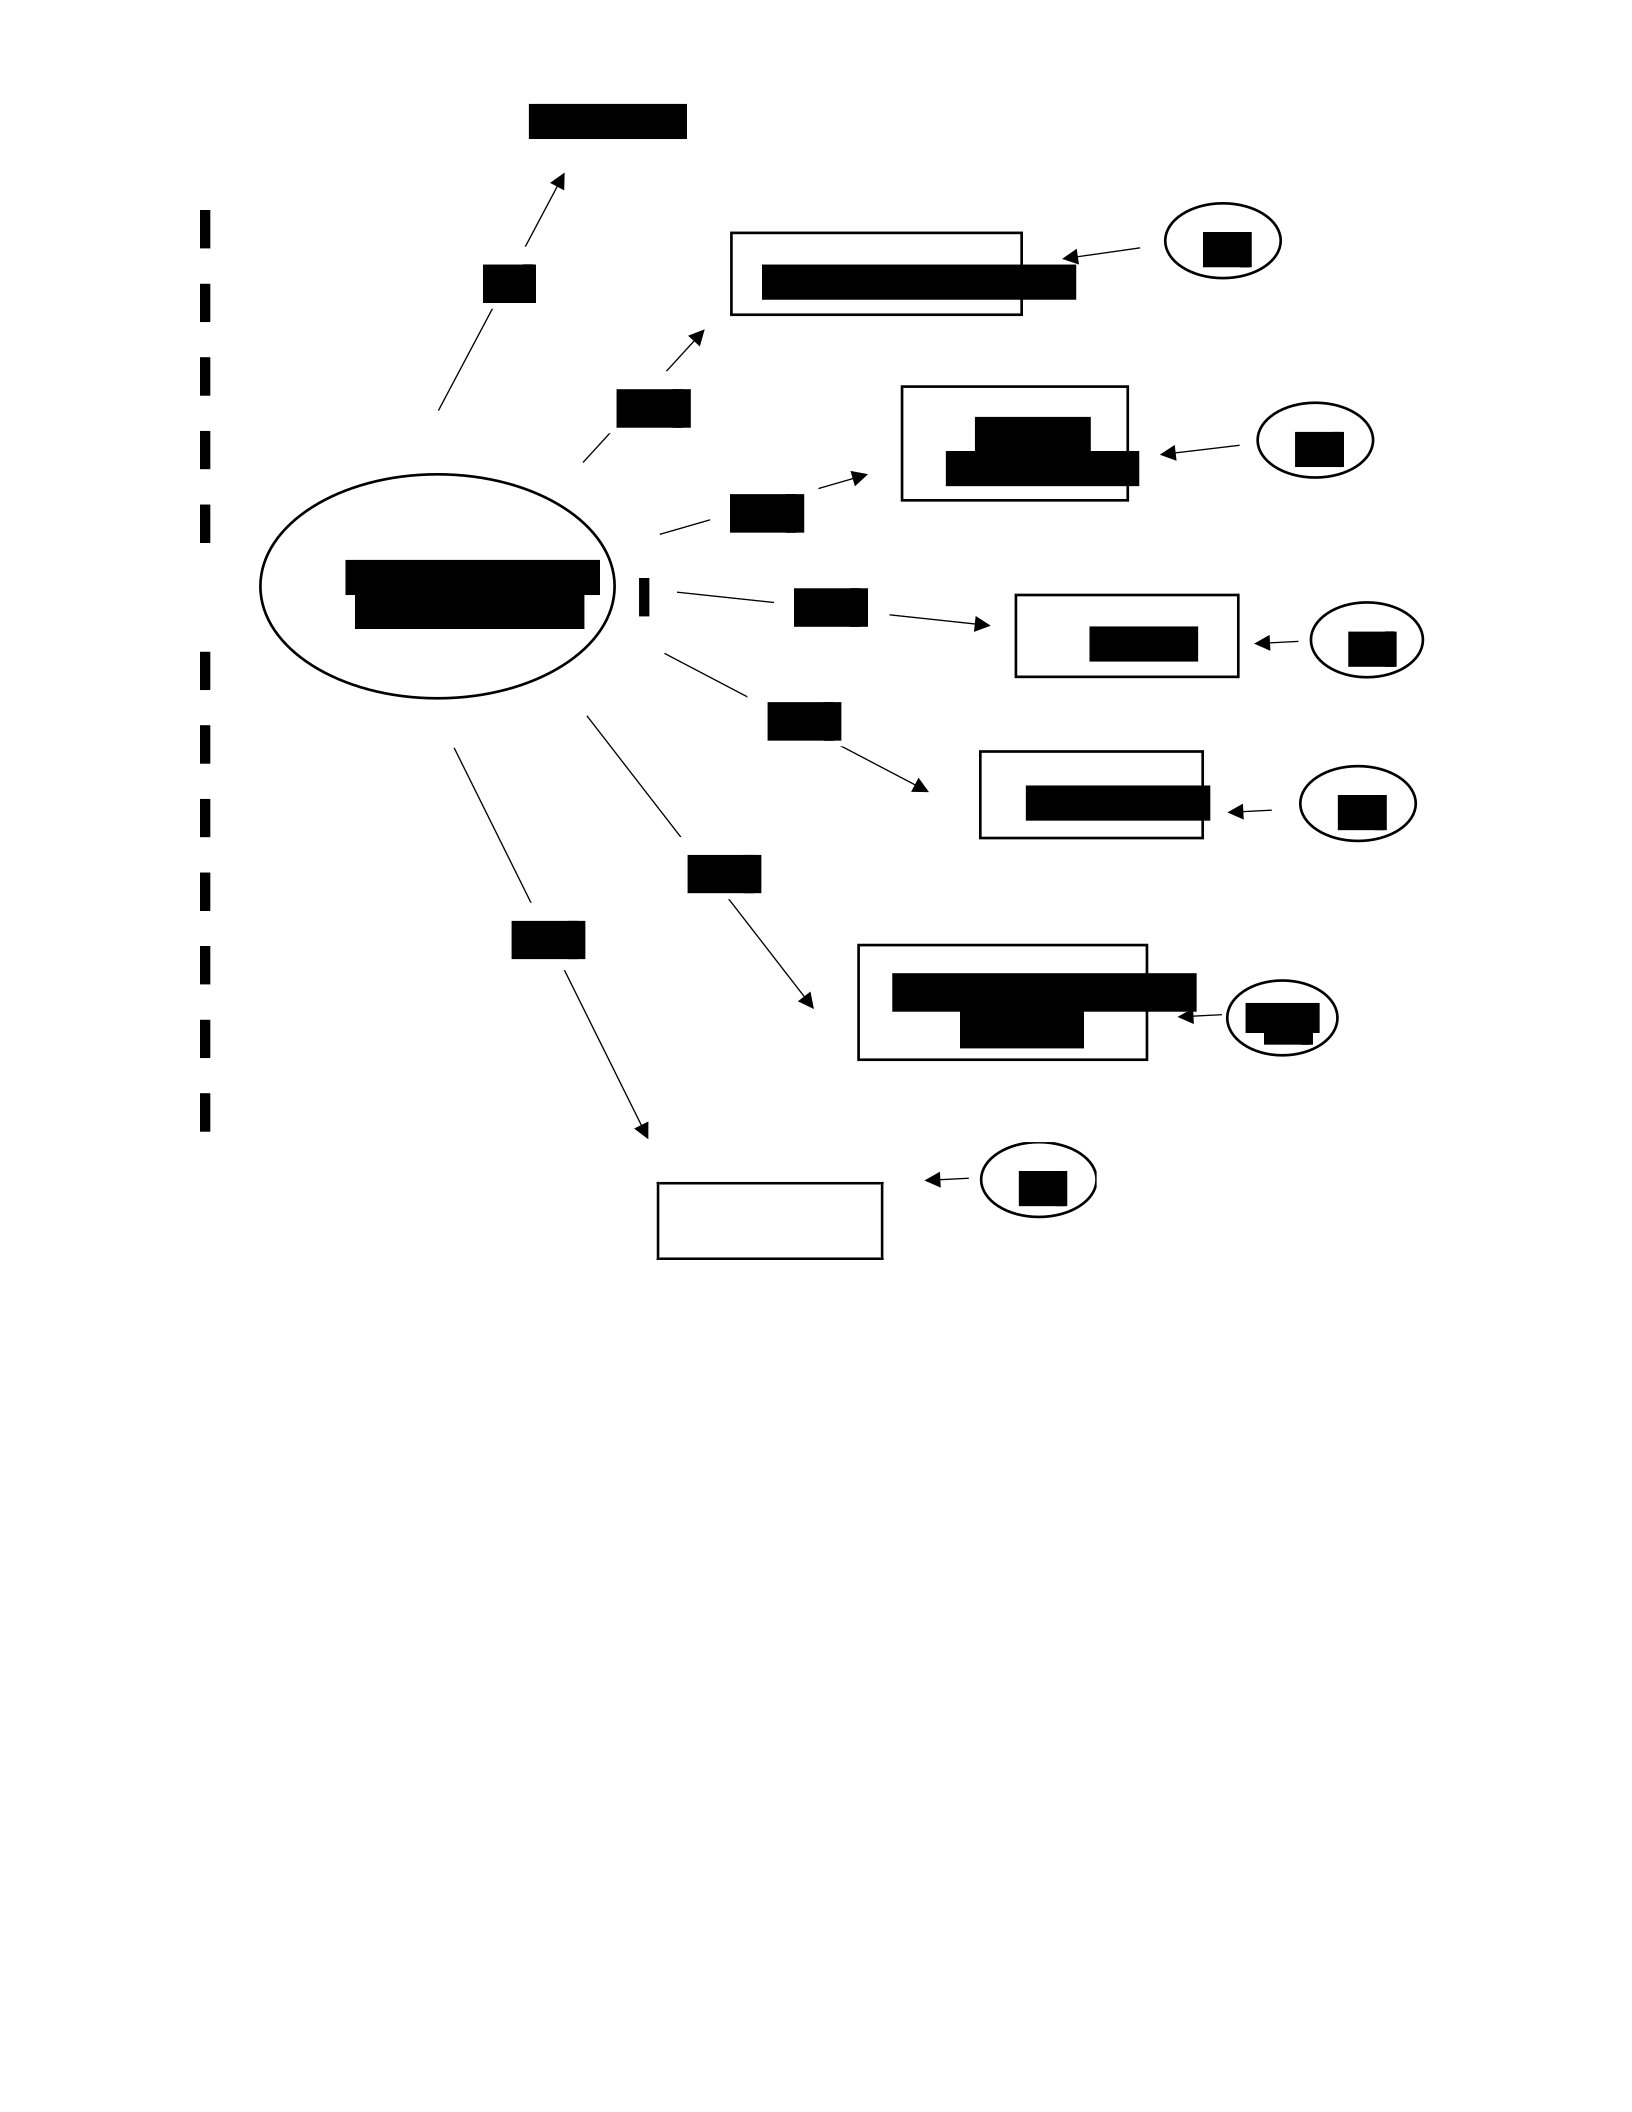
Anxiety
Figure 2.3. Confirmatory factor analysis: seven-factor model of Comprehensive Sexual Health
for Heterosexual Women with factor loadings and standard error.
Note. * p < .05
CHAPTER 3: THE IMPACT OF HETERONORMATIVITY ON QUEER WOMEN’S
COMMUNICATION PROCESSES AND COMPREHENSIVE SEXUAL HEALTH
Health disparities are present when members of a particular minoritized group (e.g.,
LGBQ women) have greater risk for, or actually experience, poorer health compared to those in
a majority group (Russell, Coleman, & Ganong, 2018). Decades of documentation suggest such
disparities are pervasive in the United States (Weinstein, Geller, Negussie, & Baciu, 2017), and
the types of health outcomes tracked range from mental health and substance abuse to sexual
.06
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction
Safety
Depression
Perceived Sexual
Health
.04
.53*
.07
.57*
.32*
.08
.06
.50*
.07
.41*
.07
.49*

health and general physical health (CDC, 2017; Weinstein et al., 2017). Unfortunately, statistics
on queer women’s (e.g., bisexual, lesbian, pansexual), sexual health are limited but do suggest
the presence of some significant sexual health disparities (Baptiste- Roberts, Oranuba, Werts, &
Edwards, 2017). Of note, we use the term queer as an umbrella term to refer to women who are
attracted to other women regardless of their self-identified sexual orientation. Because sexual
orientation is comprised of attraction, behavior, and identity, and these may not always align
(Vrangalova & Savin-Williams, 2012), the use of queer is a more inclusive approach to
capturing a range of queerness among women. Most queer sexual health programming and
research has focused exclusively on queer, cisgender men, likely due to a long-standing focus on
the HIV/AIDS crisis and their perceived risk of disease acquisition (Power, McNair & Carr,
2009). Further, most female sexual health research and programming has focused on cisgender,
heterosexual women (Baptiste-Roberts, et al., 2017), suggesting that queer women are
underexamined and underserved.
As stated, research, albeit limited, suggests queer women may be at risk for sexual health
disparities. For example, reports suggest that Human Papilloma Virus (HPV) is a common
sexually transmitted infection (STI) diagnosed in women who have sex with other women
(WSW; i.e., an umbrella term that includes queer women; CDC, 2015a). The CDC (2015a)
reports that 13%-30% of WSW have some strain of HPV. Additionally, best estimates suggest
that 36% of women who reported having a same-gender partner in their lifetime had HSV-2
antibodies (i.e., the herpes virus), which is higher than women who reported never engaging in
same-gender behavior (24%). Transmission of the herpes simplex virus (HSV-1 & HSV-2) may
be higher in same-gender sexual encounters due to the prevalence of oral sex in these sexual
relationships when compared to different-gender sexual encounters (CDC, 2015a). Although
there are few statistics on bacterial infections, queer women are still at high risk for chlamydia,
gonorrhea, syphilis, and hepatitis A, B, and C due to limited use of barrier methods in sexual

encounters (Mount Sinai Adolescent Health Center, 2017; Power et al., 2009; Knight & Jarrett,
2017).
Importantly, health is not solely determined by the absence of disease, but instead, is a
product of the larger social, structural, and political context in which some lives are more valued
than others (Ratcliff, 2017). Accordingly, health disparities often emerge. The Determinants of
Health (DoH) framework created by the World Health Organization explains how social
contextual factors, such as cultural inequities, contribute to differential health outcomes (Office
of Disease Prevention; ODPHP, 2019; WHO, 2019). It asserts that there are five DoH (i.e.,
policymaking, social factors, health services, individual behavior, and biology and genetics) that
influence the presence of health disparities. This study focuses on the influence of social factors
on individual and interpersonal sexual health processes (ODPHP, 2019).
Social factors are defined as those macro level phenomenon that may influence health,
and contribute to health disparities (ODPHP, 2019). These include, but are not limited to, social
norms and attitudes (including discrimination), availability of resources, social support, mass
media, and socioeconomic factors (ODPHP, 2019). Such influences often, but not always, are
indirect and stem from issues of cultural exclusion and inclusion. This may contribute to queer
health disparities, and more specifically sexual health disparities. For example,
heteronormativity is a social factor that privileges sexual partnering between two married,
cisgender, and heterosexually-identified individuals (van Eeden-Moorefield, 2018) and has
shaped the foundation of many of our social structures (Herek, 2004). Most sexuality education
curriculum (e.g., exclusion of queer sexual health and identities; Guttmacher Institute, 2019),
policies (e.g., adoption policies and child custody policies for queer families; van Eeden-
Moorefield, 2018), and the healthcare system (e.g., patient is often assumed to be heterosexual
unless otherwise stated; Sekoni, Gale, Manga-Atangana, Bhaduri, & Jolly, 2017; van Eeden-
Moorefield, 2018) are heteronormative. In turn, queer women are often underserved because
they fall outside of the heterosexual norm. Accordingly, queer women may find themselves with

little information about maintaining their sexual health and how to discuss it with others
(Marazzo, Coffey, and
Bingham, 2005)
Further, heteronormativity may influence individual behaviors (e.g., communication),
another DoH (ODPHP, 2019). For example, most learn that penile penetrative sexual behavior is
one of the only ways to have sexual intercourse in heterosexual relationships and carries high
sexual risk (McNeill, 2013). WSW do not typically engage in penile penetration, and therefore,
may assume that they are at lower sexual risk (Baptiste- Roberts, et al., 2017). Therefore, this
heteronormative perspective of sexual behavior and sexual risk would lead to the assumption
(both culturally and medically) that in order to have sexual risk, penile penetration is necessary.
Because of this presumption queer women may perceive they are not at risk for HIV, STIs or
unintended pregnancy and, accordingly, have reported underusing barrier methods
(BaptisteRoberts et al., 2017). Such an example demonstrates how heteronormativity can
influence individual behaviors in a way that accounts for the presence of a health disparity
among queer women. Taken together, individual behaviors can act as a mechanism through
which cultural factors influence health, and this may be a particularly salient pathway among
queer women.
To be more inclusive of queer women’s experiences, sexual health research must examine
how both individual, interpersonal, and social processes operate in determining sexual health
outcomes, especially those that represent disparities (Baptiste-Roberts et al., 2017; Weinstein et
al., 2017; ODPHP, 2019). Earlier, we describe how the cultural factor of heteronormativity might
be linked to health (Meyer, 2003). We suggested that its link is through individual behaviors.
Prior research suggests the role of sexual health communication (which may include, but is not
limited to, the discussion of one’s sexuality with another person, sexual history, concerns,
consent, and desires; Horan, 2016; Lehmiller, VanderDrift, & Kelly, 2014), may be a process
through which heteronormativity is perpetuated. For example, we know that women who

communicate about their sexual health with a potential partner are likely to engage in more safe-
sex practices, which, in turn, predicts improved sexual health outcomes (Lehmiller, et al., 2014).
This is likely due to increased discussion between partners about their sexual health histories and
discussion of safe sex preferences (Lehmiller, et al., 2014; Quinn-Nilas et al., 2016). Yet,
heteronormative messages about sexual health may indirectly lead to inaccurate health risk
perceptions in queer women (i.e., that they are not at risk for STIs) and therefore, they may not
feel the need to discuss their sexual health or engage in safe sex practices. Using focus groups,
Marazzo and colleagues (2005) examined queer women’s sexual practices and understanding of
sexual health. They found that many queer women were not well versed in preventative sexual
health measures (e.g., washing sex toys between partner usage). Those that used barrier methods
reported doing so if someone reported having an STI. Therefore, they were used, but relatively
infrequently. By improving sexual communication self-efficacy (i.e., an individual’s perception
of how well they communicate about their sexuality with a partner; Quinn-Nilas, et al. 2016)
among queer women, perhaps safe sex behaviors will improve, and queer women will have
better comprehensive sexual health outcomes. Therefore, the purpose of this study was to test a
model examining how heteronormativity influences sexual health communication self-efficacy in
queer female populations, and how that influences comprehensive sexual health outcomes. The
hypothesized model was outlined below.
Model Hypothesis
We know that there is a relationship between sexual health communication, safe sex
behaviors, and comprehensive sexual health outcomes (e.g., Quinn-Nilas et al., 2016). However,
cultural heteronormativity may alter this relationship, because queer women are left with
inaccurate information about their sexual risk (Baptiste-Roberts et al., 2017), and also there is
stigma surrounding women discussing their sexuality (Easton & Hardy, 2009). Therefore, we
hypothesized that there would be a direct relationship between sexual communication
selfefficacy and comprehensive sexual health. This relationship would be partially mediated by

safe sex behaviors since this is a mechanism to improve sexual health outcomes (CDC, 2020).
Further, heteronormativity experienced by queer women would moderate the relationship
between sexual communication self-efficacy and safe sex behaviors because queer women may
not understand the importance of discussing sexual health due to misinformation about their
sexual risk (Baptiste-Roberts et al., 2017). Heteronormativity would also moderate the
relationship between safe sex behaviors and sexual health outcomes because queer women may
choose to forgo engaging in safe sex practices due to misperceptions of risk (Marazzo et al.,
2005).
Methods
Design
This study used a 30-minute cross-sectional Internet survey design. Online surveys are
cost effective and time efficient (Urban & van Eeden-Moorefield, 2018). Online methodologies
enable more diversity by casting a wide recruitment net (van Eeden-Moorefield, Proulx, &
Pasley, 2008) and permit anonymity and/or high confidentiality of respondent identities. This is
critical when surveying about sensitive topics such as sexual health, and there may be lower
response bias (Ayling & Mewse, 2009; Urban & van Eeden-Moorefield, 2017).
Sample and Procedures
This study used a convenience sample consisting of 110 cisgender queer women between
the ages of 19 and 60 from across the United States (see Table 3.1). This meets power needs
(.90) for the analyses (G*Power). All participants reported queer attraction, ranging from only
attracted to women, to having some attraction to women but with higher attraction toward men.
The majority of the sample were White, followed by Hispanic/Latina, and Asian American
individuals. Additionally, the sample was highly educated: over a third of participants earned a
Master’s or Doctoral degree (e.g., PhD, MD) and almost half of participants reported making
over $75,000 a year.

Participants were recruited using Facebook posts on the research teams’ personal
accounts (Appendix A; Gelinas et al., 2017). Using social media to recruit participants has
become a widely used recruitment strategy due to researchers’ ability to access difficult to recruit
populations (e.g., sexual minorities; Urban & van Eeden-Moorefield, 2017). The post invited
people to participate in the study, provided a link to the informed consent (Appendix B) and
survey (Appendix C), and also asked viewers to share the post to their own pages (i.e., snowball
sampling). Those interested, clicked the link listed on the recruitment announcement and were
directed to the informed consent and beginning of the survey. Participants took the survey and in
the thank you letter (Appendix D) were notified that they had the opportunity to be entered into a
lottery, to receive a $25 gift card for their participation by providing their email on an unlinked
separate page (Appendix E). Only one survey per IP address was allowed to ensure
independence of responses (Birnbaum, 2004).
Measures
The survey asked participants about their feelings of sexual health communication
selfefficacy, safe sex behaviors they have engaged in within the past 12 months, experiences of
heteronormativity, and experiences of comprehensive sexual health over the last 12 months.
Often times, sexual health outcomes may not appear for an extended period of time (e.g. most
STIs and HIV are initially symptomless, but it is suggested that people get tested every 12
months; CDC, 2015b), and therefore, examining behaviors over a 12-month span accounts for
that. Participants were asked to report their demographic information. Sample questions included
participant age, race, ethnicity, and number of sexual partners in the last 12 months. Importantly,
scores were coded such that higher scores indicated more positive/healthier comprehensive
sexual health outcomes. This was to ensure consistency across the latent measure and also
highlights positive indicators of sexuality as opposed to negative. Therefore, heteronormativity,
anxiety, depression, sexual functioning (due to originally being a dysfunction scale) and STI
diagnoses were scored so that higher scores meant better sexual health (or lower levels of these

items). For example, anxiety was reverse scores so that higher scores indicated lower levels of
anxiety, which is indicative of better comprehensive sexual health (See Table 3.2).
Sexual communication self-efficacy. Sexual communication self-efficacy was measured
using a revised version of the Quinn-Nilas and colleagues (2016) sexual communication
selfefficacy scale. This scale measures self-efficacy of sexual communication. It was originally
intended to measure sexual communication self-efficacy in adolescents, but was adapted for use
with adult queer women. This revised 15-item scale asked participants to rate their confidence in
their ability to engage in 15 conversations with a sexual partner and was measured on a 4-point
Likert scale ranging from 1= very difficult to 4= very easy. Conversation topics (i.e., questions)
include: “Ask how many partners they have had?” and “Suggest a new sexual activity (e.g. a
new sexual position).” Scores were summed and higher scores indicated higher sexual
communication self-efficacy.
Safe sex behavior. Safe sex behavior was measured using a modified version of the Safe
Sex Behavior Questionnaire (DiIorio, 2009) which measured participant use of safe sex
behaviors. This 8-item scale was revised to only questions that were specific to sexual behaviors
and omitted questions related to substance abuse and sexual orientation. It was measured on a
4point Likert scale ranging from 1=never to 4= always. Sample questions included “I insist on
condom use when I have sexual intercourse,” and “I ask my potential sexual partners about their
sexual history.” Scores were summed and higher scores indicated more safe sex behavior.
Heteronormativity. Heteronormativity was measured using Habarth’s (2014)
Heteronormative Attitudes and Beliefs scale. This measure consisted of the Essential Sex and
Gender Subscale and the Normative Behavior Subscale within the larger scale. This 16-item
scale measuresd heteronormative attitudes and beliefs that individuals possess using a 7-point
Likert Scale (1= Strongly Disagree, 7= Strongly Agree). Sample questions include: “There are
only two sexes: male and female.” Scores were summed and higher scores indicated lower
heteronormative attitudes and beliefs.

Comprehensive sexual health. Comprehensive sexual health was a latent construct that
was measured using seven observed variables: anxiety, depression, perceived physical sexual
health, safety, sexual functioning, sexual satisfaction/pleasure, and STIs/HIV. Measures for this
construct were based off of the WHO’s (2019) definition of sexual health.
Anxiety. Anxiety was measured using a 3-item author created scale (modeled after Janda
& O’Grady’s, 1980, Sex Anxiety Inventory). This measured anxiety about sexuality and sexual
experiences. Questions were measured on a 7-point Likert scale (1= Untrue of me, 7= Very true
of me). Sample questions included “I generally felt anxious about sex with other people.” Scores
are summed and higher scores indicated less sex related anxiety.
Depression. Depression was measured using a modified version of Radloff’s (1977)
12item CESD-R scale, which measured depressive symptoms in the general population. This
10item scale was measured using a 4-point Likert Scale (1= rarely or none of the time; less than
1 day, 4= most or all of the time; 5-7 days). Participants were asked to select the number of
times they felt or behaved in the last week and sample questions included “I was bothered by
things that usually do not bother me.” Scores were summed and higher scores indicated lower
levels of depression.
Perceived physical sexual health. Perceived physical sexual health was measured using
an author created global measure which asked, “To what extent do you feel you are physically
healthy enough to have sex?” This question was measured on a 4-point Likert Scale (1= Not at
all healthy, 4=Very healthy).
Safety. Safety was measured using an author created global measure which asked
participants to “Think about the last time you engaged in sex with a partner. How safe did you
feel?” The item was scored using a 5-point Likert Scale (1= Not safe at all, 5=Very safe).
Sexual functioning. Sexual functioning was measured using a modified version (5-item
scale) of the Female Sexual Function Index (Rosen, 2000), which assesses common domains of
female sexual functioning. Desire, arousal, lubrication, orgasm, and pain are the domains of

sexual functioning that were measured. Sample questions include “How often did you find it
difficult to be aroused” (1= never, 7= always). Responses were measured on a 7-point Likert
scale; scores were summed and higher scores indicated better sexual functioning.
Sexual satisfaction/pleasure. Sexual satisfaction/pleasure was measured using the 6-item
modified version of Rosen et al., (2004) Male Sexual Health Questionnaire. This scale was
modified so that it was applicable to women. This scale assessed sexual satisfaction. Sample
questions were “How satisfied are you with the overall sexual relationships you have?”
Responses were measured on a 5-point Likert scale (1= Not at all satisfied, 5= Very satisfied).
Scores were summed and higher scores indicated higher sexual satisfaction.
STI/HIV. STI/HIV was measured using an author created questionnaire which asked
about respondent’s experiences with STI diagnoses. Respondents were asked to fill in how many
times they had been tested for STIs and HIV in the last year. They were also asked to fill in the
number of times they had Chlamydia, Gonorrhea, and/or Syphilis in the last 12 months. A
singleitem measure was used to ask if participants had herpes (because it is a treatable STI and
therefore, cannot be acquired multiple times). The question asked: Do you have herpes? Answers
included “yes, no, not sure, prefer not to answer”. A single-item measure was used to ask if they
had HIV (because this is a treatable STI and therefore, cannot be acquired multiple times). The
question asked: Do you have HIV? Answers included “yes, no, not sure, prefer not to answer.”
No women in this sample had HIV diagnoses and therefore, questions about HIV were excluded
from analysis. Since herpes can only be acquired once, scores were recoded so that “yes” = 1 and
no = 0. Number of STI diagnoses were summed and reverse scored so that higher scores
indicated better sexual health (i.e., lower STI diagnoses).
Data Analysis Plan
Data were imported into SPSS where cleaning and preliminary analyses (e.g., assessment
of normality, reliability, and missingness) occurred. Data were missing completely at random
(i.e., less than 20% of data per variable; Dong & Peng, 2013; Schumacker & Lomax, 2010).

Missing data was replaced using multiple imputation (MI) with five estimation rounds conducted
to ensure reliable estimates. MI is commonly used to account for missing data because it is able
to reliably estimate larger percentages of missing data with precise and efficient estimates
(Madley-Dowd, Hughes, Tilling, & Heron, 2019). Correlations were conducted to examine
variable relationships (See Table 3.3), which largely were as expected.
Next, a confirmatory factor analysis (CFA) of the latent construct (comprehensive sexual
health) was run to assess that the observed measures accurately measured the latent construct
(Schumacker & Lomax, 2010). Model fit was assessed here and across all other models using
several indices: Chi Square (χ2) test, Comparative Fit Index (CFI), Goodness of Fit Indices
(GFI), and Root Mean Square Error of Approximation (RMSEA; Schumacker & Lomax, 2010).
The full moderated-mediating model was tested in AMOS (Arbuckle, 2013) using ML
estimation with a mixture of observed and latent variables (Schumacker & Lomax, 2010). ML
estimation provides unbiased and strong parameter estimates (Lei & Wu, 2012). First, one
thousand bootstraps were used to test the base mediation model (Cheong & MacKinnon, 2012),
which means that random subsamples of safe sex behaviors were estimated 1,000 times to ensure
that mediation is present (Cheong & MacKinnon, 2012). Bootstrapping has been used more than
other types of resampling methods and produces strong confidence intervals.
A median split was used to determine groups that had high levels of internalized
heteronormativity vs. low levels of internalized heteronormativity. Moderation of the mediation
model was tested using multi-group analysis in AMOS (Arbuckle, 2013), comparing constrained
(i.e., theoretically based models) and unconstrained models (i.e., exploratory models; Byrne,
2010; Qureshi & Compeau, 2009; Savalei & Kolenikov, 2008).
Results
Preliminary Results
Correlations between demographic variables (e.g., age, income) and endogenous
variables were used to identify potential controls for use in the model. Participant age was

significantly correlated with feelings of safety (r(108) = .20, p < .05). Participant income was
significantly related to depression (r(108) = .32, p < .05). Finally, having insurance was
significantly related to perceived sexual health (r(108) = -.25, p < .05), depression (r(108) = .36,
p < .05), and sexual satisfaction (r(108) = .33, p < .05). When controls were added to the model,
age (p = .94) and income (p = .75) were not significantly related to comprehensive sexual health
outcomes. However, insurance was significantly related to comprehensive sexual health
outcomes and therefore, was kept in the final model as a control (p < .05). Results from the CFA
suggested strong model fit for the latent variable (See Chapter 2).
Hypothesized Model Testing
The base model was a mediation model that assessed the direct relationship between
communication self-efficacy and comprehensive sexual health and the indirect one on
comprehensive sexual health through safe sex behaviors. Model fit was strong, χ2 (31, N = 110)
= 36.03, p = .25, CFI = 0.97, GFI = .94, RMSEA = .04, and accounted for 44% of the variance in
comprehensive sexual health (see Table 3.4; Figure 3.1). Results show a strong positive
relationship between communication self-efficacy and comprehensive sexual health; when
sexual communication self-efficacy increases, comprehensive sexual health also increases.
However, indirect effects were not significant in spite of the strong model fit. This was expected
though given the model was hypothesized to be moderated.
Next, moderation of the model (i.e., high vs. low internalized heteronormativity) was
tested and results suggested moderation was present at the model level. Importantly, the model
for queer women with low internalized heteronormativity accounted for 67% of the variance in
comprehensive sexual health (R2=.67; Figure 3.2). In the model for queer women with high
internalized heteronormativity, sexual communication self-efficacy only accounted for 43% of
the variance in comprehensive sexual health outcomes (R2=.43), which is less than the base
mediation model (Figure 3.3).

First, we tested the direct link between sexual communication self-efficacy and
comprehensive sexual health for moderation using The Stats Tool Package excel file (Gaskin,
2012). This link was significantly different between those with high and low heteronormativity
(i.e., χ2 (63, N = 110) = 98.45> 96.35 which was the 95% CI threshold). Specifically, the link
between sexual communication self-efficacy and comprehensive sexual health outcomes was
significantly stronger for queer women who had low levels of internalized heteronormativity
compared to queer women with high levels of internalized heteronormativity (see Figure 3.2).
Upon further examination, we noticed the links between sexual communication self-efficacy and
safe sex behaviors was not significant for either group; thus, indirect effects remained
insignificant regardless of the level of heteronormativity and this runs counter to our
hypothesized model (i.e., χ2 (63, N = 110) = 93.04 < 95.22 which is the 90% CI threshold). A
difference in parameter estimates for the link between safe sex behavior and comprehensive
sexual health outcomes also was present, so we tested for moderation of this link. Results from
this confirmed this link also was not moderated (i.e., χ2 (63, N = 110) = 92.73 < 95.22 which is
the 90% CI threshold). It appears the magnitude of difference between groups for the direct
relationship was so strong that it made the results for model level moderation appear significant
when only one link was moderated. Stated differently, although model level moderation was
statistically present, it appears that it may not be meaningfully present. Nonetheless, this is an
important finding that is discussed below.
Discussion
This study, grounded in the DoH framework, sought to understand how heteronormativity
influences the direct and indirect links between sexual communication selfefficacy, safe sex
behaviors, and comprehensive sexual health outcomes. Notably, this study was one of the first to
use a comprehensive measurement of sexual health as opposed to studies (e.g., Painter et al.,
2012) that rely on single indicators of any of the three individual domains of sexual health (i.e.,
physical, mental, social; WHO, 2019). Secondly, it did so with a focus on queer women, a group

whose sexual health is not well understood in spite of being a group at particular risk to
experience health disparities (Marazzo et al., 2005). Results partially supported our hypothesized
moderated mediation model, although not entirely as expected. Specifically, the results of this
study suggested communication self-efficacy played more of a direct role in explaining variation
in comprehensive sexual health rather than an indirect role through engagement in safe sex
behaviors. Additionally, the link between sexual communication selfefficacy and comprehensive
sexual health, although significant for both groups, was significantly stronger for queer women
with low internalized heteronormativity than for those who had high internalized
heteronormativity. In other words, queer women who had low internalized heteronormativity and
high sexual communication self-efficacy were more likely to have higher comprehensive sexual
health. For queer women, with high internalized heteronormativity, the positive relationship
between sexual communication self-efficacy and comprehensive sexual health outcomes was not
as strong.
As hypothesized, sexual communication self-efficacy significantly predicted
comprehensive sexual health outcomes. This makes sense because it is well established within
the literature that communication between partners has been found to foster closeness and
emotional intimacy within romantic relationships, ultimately enhancing relationship satisfaction
(Yoo, Bartle-Haring, Day, and Gangamma, 2013). Additionally, sexual communication when
compared to general communication, has been found to predict sexual satisfaction, which is an
important indicator of comprehensive sexual health (Montesi, Fauber, Gordon, and Heimberg,
2010). Using surveys, Montesi and colleagues (2010) examined how general communication and
sexual communication contributed to sexual and relationship satisfaction. They found that sexual
communication was very important for sexual satisfaction, and that general communication only
impacted general relationship satisfaction. Thus, supporting the strong predictive relationship of
sexual communication self-efficacy and comprehensive sexual health outcomes.

However, results did not support the hypothesized indirect relationship of sexual communication
self-efficacy and comprehensive sexual health outcomes through safe sex behaviors. First, the
previous research that suggested safe sex behaviors mediate the relationship between sexual
communication self-efficacy and sexual health outcomes has largely focused on heterosexual
samples (e.g., Holland & French, 2012) or men who have sex with other men (MSM; Lapinski,
Braz, and Maloney, 2010) overlooking queer women’s unique sexual health experiences within
the context of heteronormativity. When we consider queer women, research suggests an
interaction between heteronormativity and safe sex behaviors (e.g., women with high levels of
internalized heteronormativity may not use safe sex behaviors due to misinformation about
sexual risk; Marazzo et al., 2005), thus, leading us to hypothesize a moderated mediation model.
Therefore, it is not surprising that mediation of the base model was not significant for this
specific group. As researchers, it is important to understand how these sexual health processes
occur within the larger heteronormative context for different intersections to truly begin to
understand nuances of comprehensive sexual health outcomes across diverse populations
(Santos, Williams, Rodriguez, and Ornelas, 2017).
That being said, results partially supported our hypothesis that heteronormativity would
completely moderate the mediation model. The direct relationship between sexual
communication self-efficacy and comprehensive sexual health outcomes was significantly
stronger for queer women with low internalized heteronormativity when compared to queer
women with high internalized heteronormativity. This is in line with previous research that
suggests queer women who have low internalized heteronormativity would ascribe less to the
stigma perpetuated by heteronormative culture (i.e., that women should not be sexual and
homophobia). For example, perhaps queer women with high internalized heteronormativity have
adopted intrusive thoughts that hinder their ability to communicate with a partner (Lewis,
Derlega, Clarke, & Kuang, 2006). Lewis and colleagues (2006) examined how lesbian women
who had high stigma consciousness and social constraints (which heteronormativity

perpetuates), had intrusive thoughts, internalized homophobia, and actual physical symptoms
related to awareness of heteronormative based discrimination. Therefore, perhaps for women
with high internalized heteronormativity, adding an indicator to this model that asked women
about their awareness of cultural stigma would present a clearer picture of the relationship
between communication self-efficacy and comprehensive sexual health.
Yet, even though the link between sexual communication self-efficacy and
comprehensive sexual health was significantly stronger for women with low internalized
heteronormativity, the link still remained significant across both groups. Previous research
suggests that queer women have strong sexual communication leading to better sexual health
outcomes (Frederick, John, Garcia, & Lloyd, 2018). Frederick and colleagues (2017) examined
orgasm frequency among gay, lesbian, bisexual and heterosexual men and women. They found
that queer women had more orgasms than heterosexual women. Importantly, they found that
women who had more orgasms were more likely to communicate about their sexual preferences
and praise their partner for sexual actus. Therefore, perhaps sexual communication is a strength
of queer women. Since there are two women involved, the gendered communication that would
be present in a different gender sexual encounter is not present (D’Emilio & Freedman, 2012)
potentially promoting more open communication. It is important to note that this information is
specific to women who have sex with women, and in this study we examined women who are
attracted to other women. Thus, this may not fully explain what is occurring in our sample, but is
a theory that would be applicable. Therefore, even though heteronormativity may reduce the
strength of the link between sexual communication self-efficacy and comprehensive sexual
health outcomes, it is still somewhat strong and significant for queer women across both models.
Finally, regardless of level of internalized heteronormativity, the indirect relationship
between sexual communication self-efficacy, safe sex behaviors, and comprehensive sexual
health outcomes was not significant. In line with previous research, perhaps heteronormative
scripts suggesting that queer women are not at risk for negative sexual health outcomes (i.e.,

STIs, unintended pregnancy; Marazzo et al., 2005) was so strong that even women who had high
sexual communication self-efficacy did not discuss or engage in safe sex behaviors. Using
qualitative interviews, Santos and colleagues (2017) examined young Latina queer women’s
sexual health. They found that women perceived their sexual health was largely shaped by
cultural context (e.g., a multiple minority status based on sexual identity, ethnicity, and gender).
Within this context, they reported that their sex education was largely heteronormative (i.e.,
discussed sex in the context of two heterosexual people in love), and these women often found
themselves without information on risk and protection for queer women. Additionally, women
reported perceptions of less risk when engaging in sexual behavior with a cisgender female
partner when compared to cisgender male partner. Therefore, this lack of risk perception may
completely mitigate queer women’s use of safe sex behaviors, suggesting no indirect effect.
Taken together, sexual health processes must be examined with cultural context in mind.
The indirect effect of sexual communication self-efficacy, safe sex behaviors, and
comprehensive sexual health outcomes are well supported in the literature (e.g., Donne, Hoeks,
& Jansen, 2017). Although this relationship may exist for some populations, it does not exist for
all. Specifically, for queer women, sexual communication self-efficacy may be more important
for comprehensive sexual health outcomes, because there are such large misconceptions about
queer women and sexual risk (Baptiste-Roberts, et al., 2017). Additionally, the strength of the
predictive relationship of sexual communication self-efficacy and safe sex behaviors varies
based on women’s internalization of heteronormativity. Therefore, as we begin to parse what
factors contribute to comprehensive sexual health outcomes for diverse groups of people, we
must also take into consideration cultural context and its influence on individual and
interpersonal processes.
Limitations
This study but be considered within the bounds of its limitations. The first major
limitation of this study is that the sample lacked diversity. Specifically, the sample was largely

White, highly educated, and made over $75,000. Therefore, these results cannot be generalized
to more diverse populations. This is a shortcoming of sampling through social media friend
networks, because most people are likely to be friends with individuals who are similar to them
(Naruchitparames, Gunes, & Louis, 2011). To recruit more diverse samples for health research,
the NIH (2020) suggests targeting survey recruitment to specific populations on Facebook. Thus,
future research should consider ways to ensure diversity across their samples. By employing this
model with more diverse populations, we can understand how these sexual health processes
function across divers intersections. Additionally, this study utilized queer attraction rather than
queer identity or behavior (Vrangalova & Savin-Williams, 2012). This was to be inclusive of the
broad definition of queer. However, same gender attraction does not necessarily mean that
someone will engage in sexual behavior with someone of the same gender, and therefore, it
poses challenges to measuring physical health outcomes. Therefore, it would be beneficial to use
this model with women who identify as queer as well as women who have sex with other
women, regardless of their identities.
References
Arbuckle, J. L. (2013). Amos 22 user’s guide. Chicago, IL: SPSS.
ASHA. (2019). Women & STIs. Retrieved on April 11, 2019 from
http://www.ashasexualhealth.org/sexual-health/womens-health/women-and-stis/
Ayling, R., & Mewse, A. J. (2009). Evaluating internet interviews with gay men. Qualitative
Health Research, 19(4), 566-576. doi: 10.1177/1049732309332121
Baptiste-Roberts, K., Oranuba, E., Werts, N., & Edwards, L. V. (2017). Addressing healthcare
disparities among sexual minorities. Obstetrics and Gynecology Clinics of North
America, 44, 71-80. doi: 10.1016/j.ogc.2016.11.003
Birnbaum, M. H. (2004). Human research and data collection via the internet. Annual Review of
Psychology, 55, 803-832. doi: 10.1146/annurev.psych.55.090902.141601

Byrne, B. M. (2010). Structural equation modeling with AMOS: Basic concepts, applications,
and programming (3rd ed.). New York, United States: Routledge Taylor & Francis
Group.
CDC. (2015b). Which STD test should I get? Sexually Transmitted Diseases (STDs). Retrieved
on June 3, 2019 from https://www.cdc.gov/std/prevention/screeningreccs.htm
CDC. (2015a). Special populations. 2015 Sexually Transmitted Diseases Treatment Guidelines.
Retrieved May 29. 2019 from https://www.cdc.gov/std/tg2015/specialpops.htm#WSW
CDC. (2017). STD health equity. Retrieved on May 9, 2019 from
https://www.cdc.gov/std/health-disparities/default.htm
CDC. (2020). Sexual risk behaviors can lead to HIV, STDs, & Teen pregnancy. Retrieved on
April 18, 2020 from https://www.cdc.gov/healthyyouth/sexualbehaviors/index.htm
Cheong, J., & MacKinnon, D. P. (2012). Mediation/ indirect effects in structural equation
modeling. In R. H. Hoyle (Ed.), Handbook of Structural Equation Modeling (425-436).
New York, United States: The Guildford Press.
DiIorio, C. (2009). Safe sex behavior questionnaire. In T. D. Fisher, C. M. Davis, W. L. Yarber,
& S. L. Davis (Eds.), Handbook of sexuality-related measures (pp.594-596). New York,
NY: Routledge.
Dong, Y., & Peng, C. J. (2013). Principled missing data methods for researchers. Springerplus,
2, 222. doi: 10.1186/2193-1801-2-222
Donne, L., Hoeks, J., & Jansen, C. (2017). Using a narrative to spark safe sex communication.
Health Education Journal, 76(6), 635-647. doi: 10.1177/0017896917710967
Easton, D., & Hardy, J. W. (2009). The ethical slut. A practical guide to polyamory, open
relationships, and other adventures (2 ed). Berkeley, CA: Celestial Arts.
Frederick, D. A., John, H. K. S., Garcia, J. R., & Lloyd, E. A. (2018). Differences in orgasm
frequency among gay, lesbian, bisexual, and heterosexual men and women in a U.S.
national sample. Archives of Sexual Behavior, 47, 273-288. doi: doi: 10.1007/s10508-

017-0939-z
Gaskin, J. (2012). The Stats Tools Package. [excel file]
Gelinas, L., Pierce, R., Cohen, I. G., Lynch, H. F., & Bierer, B. E. (2017). Using social media as
a research recruitment tool: Ethical issues and recommendations. The American Journal
of Bioethics, 17(3), 3-14. doi: 10.1080/15265161.2016.1276644
Guttmacher Institute. (2019). Unintended pregnancy in the United States. Retrieved on May 3,
2019 from https://www.guttmacher.org/fact-sheet/unintended-pregnancy-united-states
Habarth, J. M. (2014). Development of the heteronormative attitudes and beliefs scale.
Psychology & Sexuality, 1-24. doi: 10.1080/19419899.2013.876444
Herek, G. M. (2004). Beyond “homophobia”: Thinking about sexual prejudice and stigma in the
twenty-first century. Sexuality Research & Social Policy, 1(2), 6-24. doi:
10.1525/srsp.2004.1.2.6
Holland, K. J., & French, S. E., (2012). Condom negotiation strategy use and effectiveness
among college students. Journal of Sex Research, 49(50), 443-453. doi:
10/1080/00224499.2011.568128
Horan, S. M. (2016). Further understanding sexual communication: Honesty, deception, safety,
and risk. Journal of Social and Personal Relationships, 33(4), 449-468. doi:
10.1177/0265407515578821
Janda, L. H. & O’Grady, K. E. (1980). Development of a sex anxiety inventory. Journal of
Consulting and Clinical Psychology, 48, 169-175. doi: 10.1037/t02581-000
Knight, D. A., & Jarrett, D. (2017). Preventative health care for women who have sex with
women. American Association of Family Physicians. Retrieved on April 1, 2019 from
https://www.aafp.org/afp/2017/0301/p314.pdf
Lapinski, M. K., Braz, M. E., & Maloney, E. K. (2010). The down low, social stigma, and risky
sexual behaviors: Insights from African-American men who have sex with men. Journal
of Homosexuality, 57(5), 610-633. doi: 10.1080/00918361003712020

Lehmiller, J. J., VanderDrift, L. E., & Kelly, J. R. (2014). Sexual communication, satisfaction,
and condom use behavior in friends with benefits and romantic partners. Journal of Sex
Research, 51, 74-85. doi: 10.1080/00224499.2012.719167
Lei, P., & Wu, Q. (2012). Estimation in structural equation modeling. In R. H. Hoyle (Ed.),
Handbook of Structural Equation Modeling (pp.164-180). New York, United States: The
Guildford Press.
Lewis, R. J., Derlega, V. J., Clarke, E. G., & Kuang, J. C. (2006). Stigma consciousness, social
constraints, and lesbian well-being. Journal of Counseling Psychology, 53, 48-56.
https://doi.org/10.1037/0022-0167.53.1.48
Madley-Dowd, P., Hughes, R., Tilling, K., & Heron, J. (2019). The proportion of missing data
should not be used to guide decisions on multiple imputation. Journal of Clinical
Epidemiology, 110, 63-73. https://doi.org/10.1016/j.jclinepi.2019.02.016
Marazzo, J. M., Coffey, P., & Bingham, A. (2005). Sexual practices, risk perception and
knowledge of sexually transmitted disease risk among lesbian and bisexual women.
Perspectives of Sexual and Reproductive Health, 31, 6-12. doi: 10.1363/psrh.37.006.05
McGinnis, J., & Harel, O. (2016). Multiple imputation in three or more stages. Journal of
Statistic Planning and Inference, 176, 33-51. doi: 10.1016/j.jspi.2016.04.001
McNeill, T. (2013). Sex education and the promotion of heteronormativity. Sexualities, 16(7),
826-846. doi: 10.1177/1363460713497216
Meyer, I. (2003). Prejudice, social stress, and mental health in lesbian, gay, and bisexual
populations: Conceptual issues and research evidence. Psychology of Sexual Orientation
and Gender Diversity, 1(S), 3-26. doi: 10.1037/2329-0382.1.S.3
Montesi, J. L., Fauber, R. L., Gordon, E. A., & Heimberg, R. G. (2010). The specific importance
of communicating about sex to couples’ sexual and overall relationship satisfaction.
Journal of Social and Personal Relationships, 28(5), 591-609.
doi:10.1177/0265407510386833
Mount Sinai Adolescent Health Center. (2017). You asked it: Do lesbians get STIs? Retrieved on

April 2, 2019 from https://teenhealthcare.org/blog/you-asked-it-do-lesbians-get-stis/
ODPHP. (2019). Determinants of Health. Retrieved on April 11, 2019 from
https://www.healthypeople.gov/2020/about/foundation-health-measures/Determinants-of-
Health#individual%20behavior
Power, J., McNair, R., & Carr, S. (2009). Absent sexual scripts: Lesbian and bisexual women’s
knowledge, attitudes and action regarding safer sex and sexual health information.
Culture, Health & Sexuality, 11, 67-81. doi: 10.1080/13691050802541674
Qureshi, I., & Compeau, D. R. (2009). Assessing between-group differences in information
systems research: A comparison of covariance- and component-based SEM. Management
Information Systems Quarterly, 33(1), 197-214. doi: 10.2307/20650285
Quinn-Nilas, C., Milhausen, R. R., Breuer, R., Bailey, J., Pavlou, M., DiClemente, R. J., &
Wingood, G. M. (2016). Validation of the sexual communication self-efficacy scale.
Health Education and Behavior, 43(2), 165-171. doi: 10.1177/1090198115598986
Radloff, L. S. (1977). The CES-D scale: A self-report depression scale for research in the general
population. Applied Psychological Measurement, 1, 385-401. doi: 10.13072/midss.120
Ratcliff, K. S. (2017). Social determinants of health. The Social Determinants of Health:
Looking
Upstream (pp. 6-24). Cambridge, UK: Polity.
Rosen, R. C., Catania, J., Pollack, L., Althof, S., O’Leary, M., & Seftel, A. D. (2004). Male
sexual health questionnaire (MSHQ): Scale development and psychometric validation.
Adult Urology, 64, 777- 782. doi: 10.1016/j.urology.2004.04.056
Rosen, R., Brown, C., Heiman, J., Leiblum, S., Meston, C., Shabsign, R., ... D’Agostino, R.
(2000). The female sexual function index (FSFI): a multidimensional self-report
instrument for the assessment of female sexual function. Journal of Sexuality and Marital
Therapy, 26(2), 191-208. doi: 10.1080/009262300278597

Russell, L. T., Coleman, M., & Ganong, L. (2018). Conceptualizing family structure in a social
determinants of health framework. Journal of Family Theory & Review, 10, 735-748.
doi: 10.1111/jftr.122
Santos, C., A., Williams, E. C., Rodriguez, J., & Ornelas, I. J. (2017). Sexual health in social and
cultural context: A qualitative study of young Latina lesbian, bisexual, and queer women.
Journal of Racial and Ethnic Health Disparities, 4(6), 1206-1213. doi: 10.1007/s40615-
016-0327-8
Savalei, V., & Kolenikov, S. (2008). Constrained versus unconstrained estimation in structural
equation modeling. Psychological Methods, 13(2), 150-170. doi: 10.1037/1082-
989X.13.2.150
Schumacker, R. E., & Lomax, R. G. (2016). A beginner’s guide to structural equation modeling
(4th ed). New York, United States: Routledge, Taylor, & Francis Group.
Sekoni, A. O., Gale, N. K., Manga-Atangana, B., Bhaduri, A., & Jolly, K. (2017). The effects of
educational curricula and training on LGBT-specific health issues for healthcare students
an professionals: A mixed-method systematic review. Journal of International AIDS and
Society, 20, 216-224. doi: 10.7448/IAS.20.1.21624
Shin, T., Davison, M. L. & Long, J. D. (2017). Maximum likelihood versus multiple imputation
for missing data in small longitudinal samples with nonnormality. Journal of
Psychological Methods, 22(3), 426-449. doi: 10.1037/met0000094
Urban, J. B., & van Eeden-Moorefield, B. M. (2018). Designing and proposing your research
project. Washington, DC: American Psychological Association.
van Eeden-Moorefield, B. (2018). Introduction to the special issue: Intersectional variations in
the experiences of queer families. Family Relations, 67, 7-11. doi: 10.1111/fare.1230 van Eeden-
Moorefield, B., Proulx, C., & Pasley, K. (2008). A comparison of internet and faceto-face (FTF)
qualitative methods in studying the relationships of gay men. Journal of
GLBT Family Studies, 4(2), 181- 204. doi: 10.1080/15504280802096856
Vrangalova, Z., & Savin-Willliams, R. C. (2012). Mostly heterosexual and mostly gay/lesbian:
Evidence for new sexual orientation identities. Archives of Sexual Behavior, 41, 85-101.
doi: 10.1007/s10508-012-9921-y.
Weinstein, J. N., Geller, A., Negussie, Y., & Baciu (2017). Communities in action. Washington,
DC: The National Academies Press. doi: 10.17226/24624
WHO. (2019). The determinants of health. Retrieved on April 11, 2019 from
https://www.who.int/hia/evidence/doh/en/
Yoo, H., Bartle-Haring, S., Day, R. D., & Gangamma, R. (2014). Couple communication,
emotional and sexual intimacy, and relationship satisfaction. Journal of Sex and Marital
Therapy, 40(4), 275-293. doi: 10.1080/0092623X.2012.751072
Table 3.1
Participant Demographic Characteristics
Variable
Percent
Race
White
90.90%
Hispanic/Latina
6.40%
East Asian/ Asian American
2.70%
Black/ African American
1.80%
South Asian/ Indian American
1.80%
Hawaiian/ Pacific Islander
<1.00%
Middle Eastern/ Arab American
<1.00%
Native American/ Alaska Native
<1.00%
Education
High School
5.50%
Some College
16.40%
Associate’s Degree
6.40%
Bachelor’s Degree
31.80%
Master’s Degree
25.50%
PhD, MD, DO, or advanced graduate work
13.60%
Other
<1.00%
Income
< $25,000
10.90%
$25,000-$49,999
20.00%

$50,000-$74,999
20.90%
$75,000-$99,999
16.40%
$100,000-124,999
14.50%
> $125,000
17.30%
Attraction
Mostly Males
64.5%
Equal Females & Males
13.60%
Mostly Females
10.90%
Only Females
8.20%
Not sure
2.70%
Health Insurance
Yes
94.50%
No
5.50%
Table 3.2
Measurement Descriptive Statistics
Measure
Minimum
Maximum
M(SD)
α
SCSE
15
60
46.77(9.31)
.92
SSB
8
30
18.14(4.66)
.64
Het*
39
112
93.60(15.75)
.91
Anx*
3
18
17.46(4.11)
.73
Dep*
14
39
29.36(6.76)
.89
PSH
1
4
3.65(.62)
---
Safe
2
5
4.80 (.51)
---
SFW*
9
34
23.35(6.05)
.83
SexSat
6
30
19.75(7.04)
.94
STI*
0
6
5.71(.89)
.81
Note. *Scales were recoded so that higher scores indicate better sexual health.
SCSE= sexual communication self-efficacy, SSB= safe sex behaviors, Het=
heteronormativity, Anx= Anxiety, Dep= Depression, PSH= perceived physical sexual health,
safe= safety, SFW= sexual functioning, SexSat= sexual satisfaction, STI= Sexually transmitted
infections
Table 3.3
Correlation of Variables

Measure
SCSE
SSB
Het
Anx
Dep
PSH
Safe
SFW
SexSat
STI
SCSE
--
SSB
-.01
--
Het^
.03
-.02
--
Anx^
.38**
-.19
.65
--
Dep^
.13
-.03
-.08
.42**
--
PSH
.10
-.06
.09
.40**
.04
--
Safe
.43**
-.08
-.07
.27**
.17
.27**
--
SFW^
.32**
-.13
.14
.46**
.21*
.31**
-.05
--
SexSat
.49**
-.14
.21
.53**
.38
.33**
.35**
.53**
--
STI^
-.01
.11
-.05
-.03
.10
-.01
.02
-.08
.01
--
Note. * p<.05, **p<.001
^ Scales were recoded so that higher scores indicate better sexual health.
SCSE= sexual communication self-efficacy, SSB= safe sex behaviors, Het=
heteronormativity, Anx= Anxiety, Dep= Depression, PSH= perceived physical sexual health,
safe= safety, SFW= sexual functioning, SexSat= sexual satisfaction, STI= Sexually transmitted
infections

HETERONORMATIVITY AND SEXUAL HEALTH 66
Table 3.4.
Unstandardized estimates, standardized estimates, and standard errors of the based mediation model, low heteronormativity model,
and high heteronormativity model.
Paths
Un.
Base Model
Stand.
S.E.
Low Heteronormativity High Heteronormativity
Un. Stand. S.E. Un. Stand. S.E.
SSB CSE
-.00
-.00
.05
.04
.07
.07
-.04
-.07
.06
Compsex SSB
-.20
-.16
.10
-.23
-.186
.12
-.33*
-.28*
.03
Compsex CSE
.37*
.60*
.06
.52*
.81*
.06
.25*
.44*
.08
Insur CSE
-5.7*
-.23*
2.13
-.62
-.02
2.55
-8.67*
-.381*
2.96
Note. * indicates p<.05
Un. = Unstandardized, Stand. = Standardized
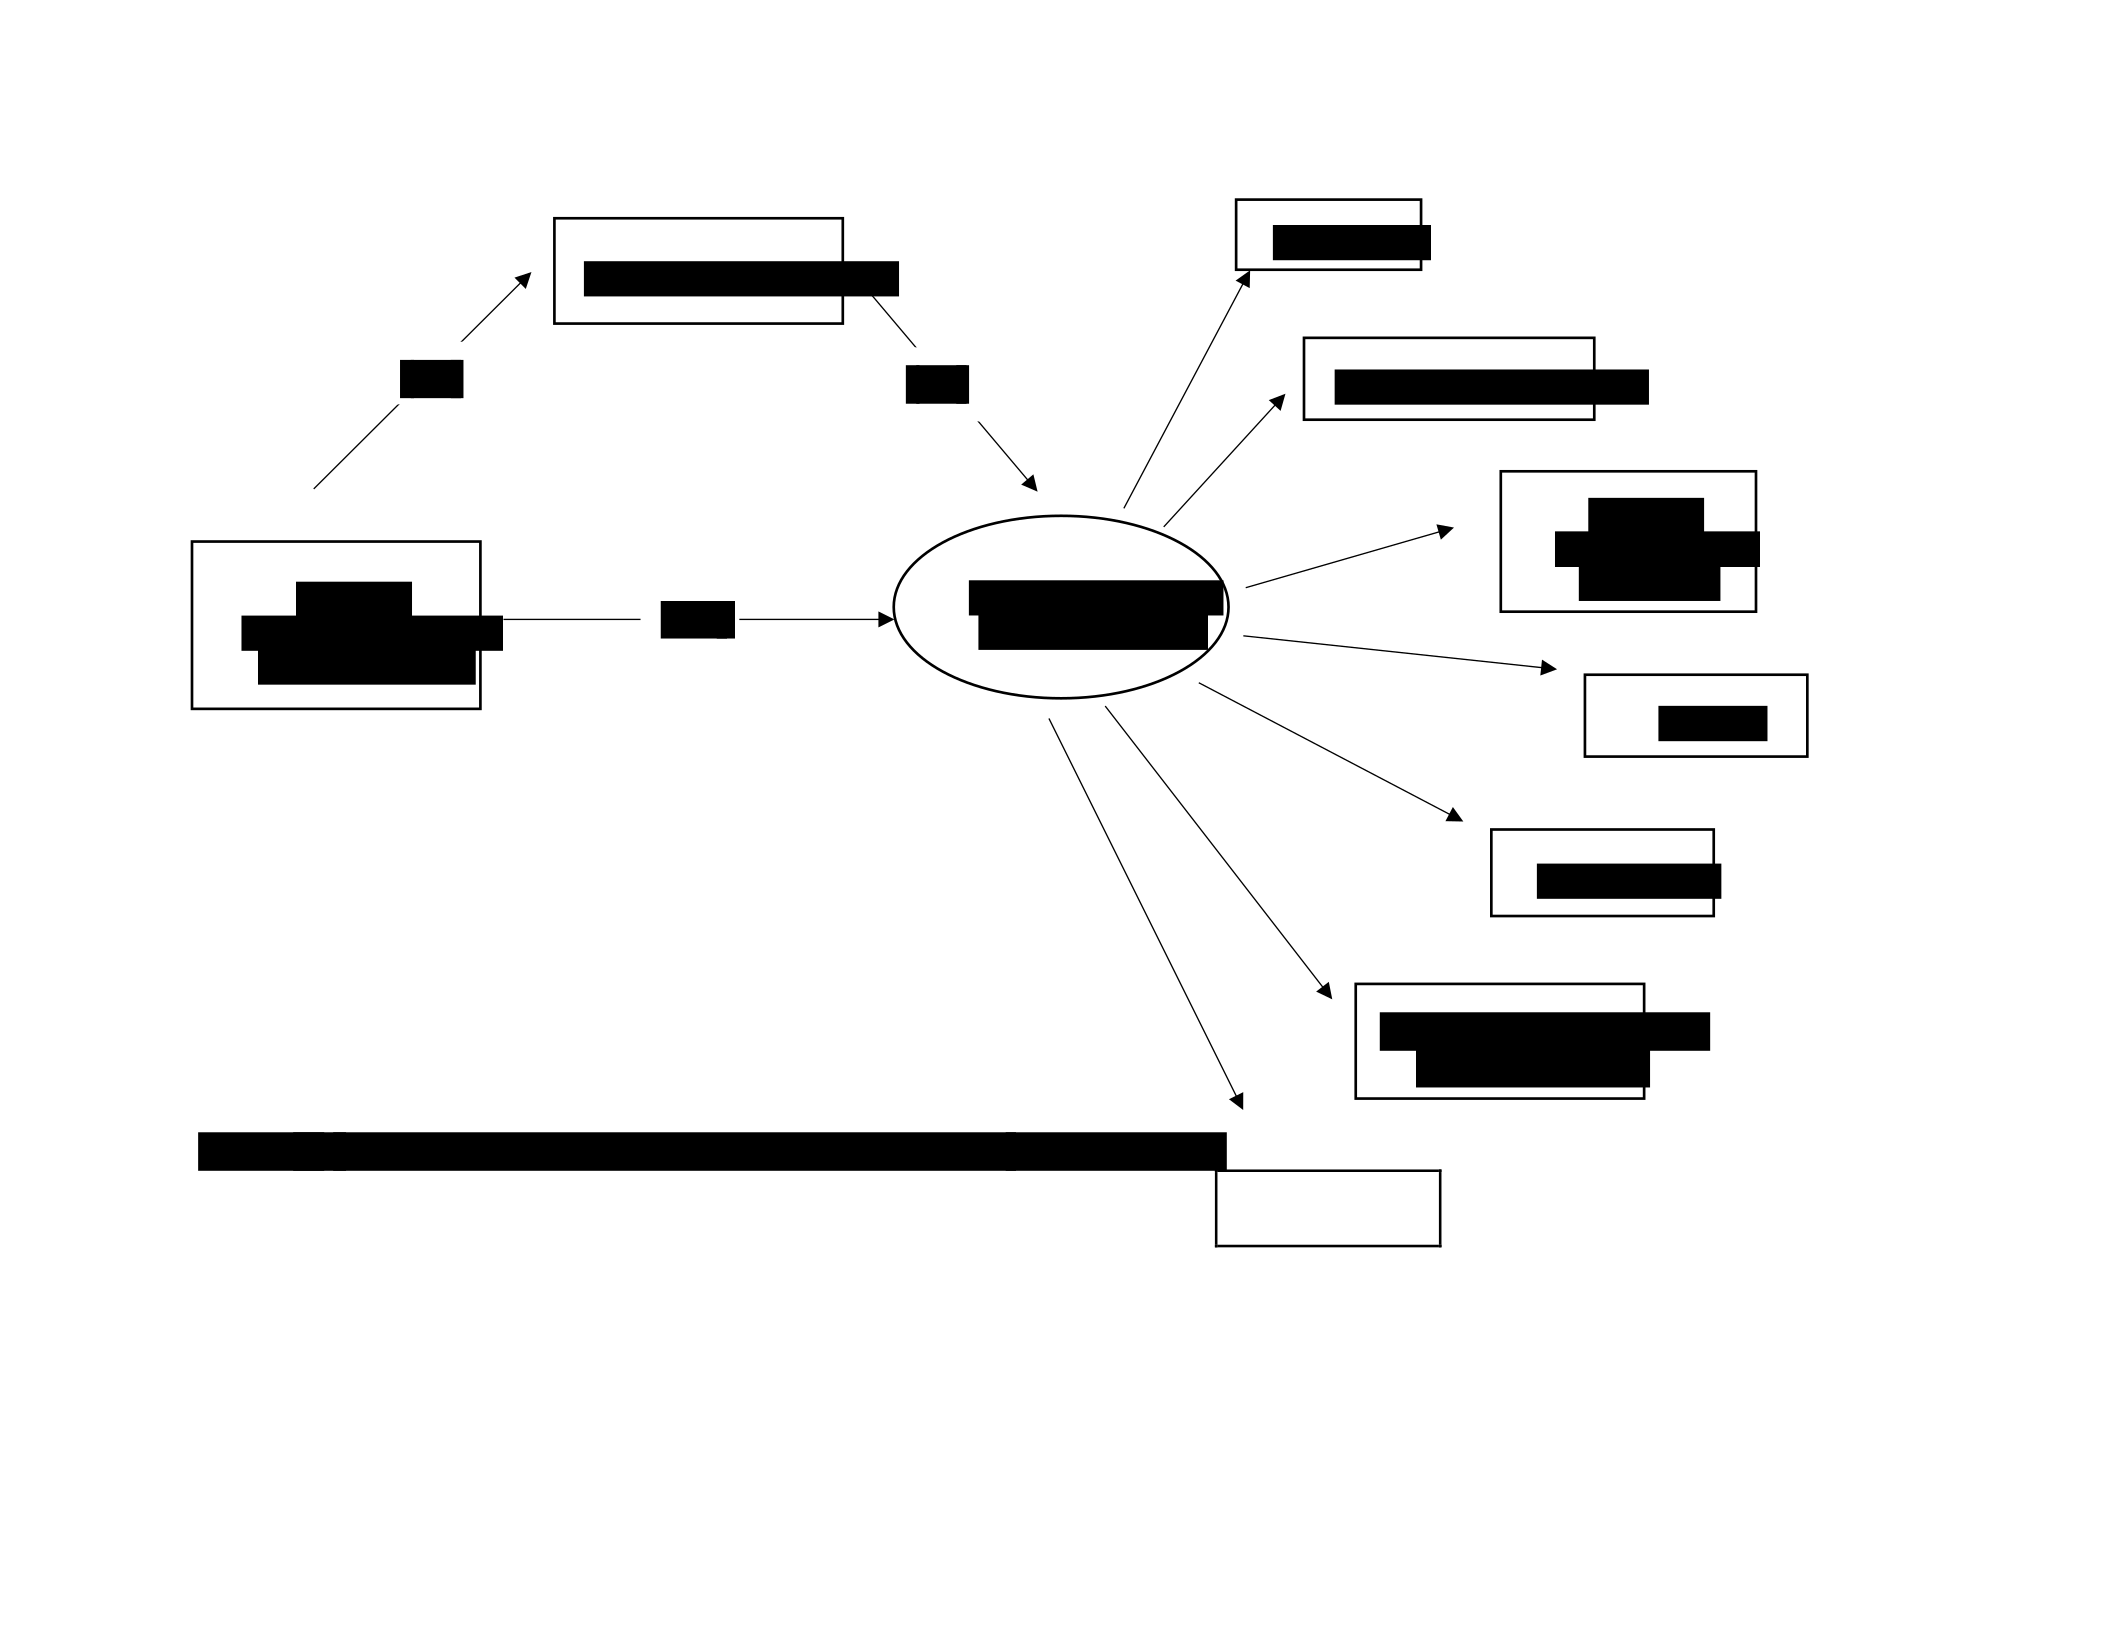
HETERONORMATIVITY AND SEXUAL HEALTH 67
Note. * indicates significant path, p < .05
Anxiety
Sexual
Communication
Self-Efficacy
Safe Sex Behaviors
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived physical
sexual health
.60*
-
.00
-
.16
Figure
3.1
. Base mediation model with standardized estimates.
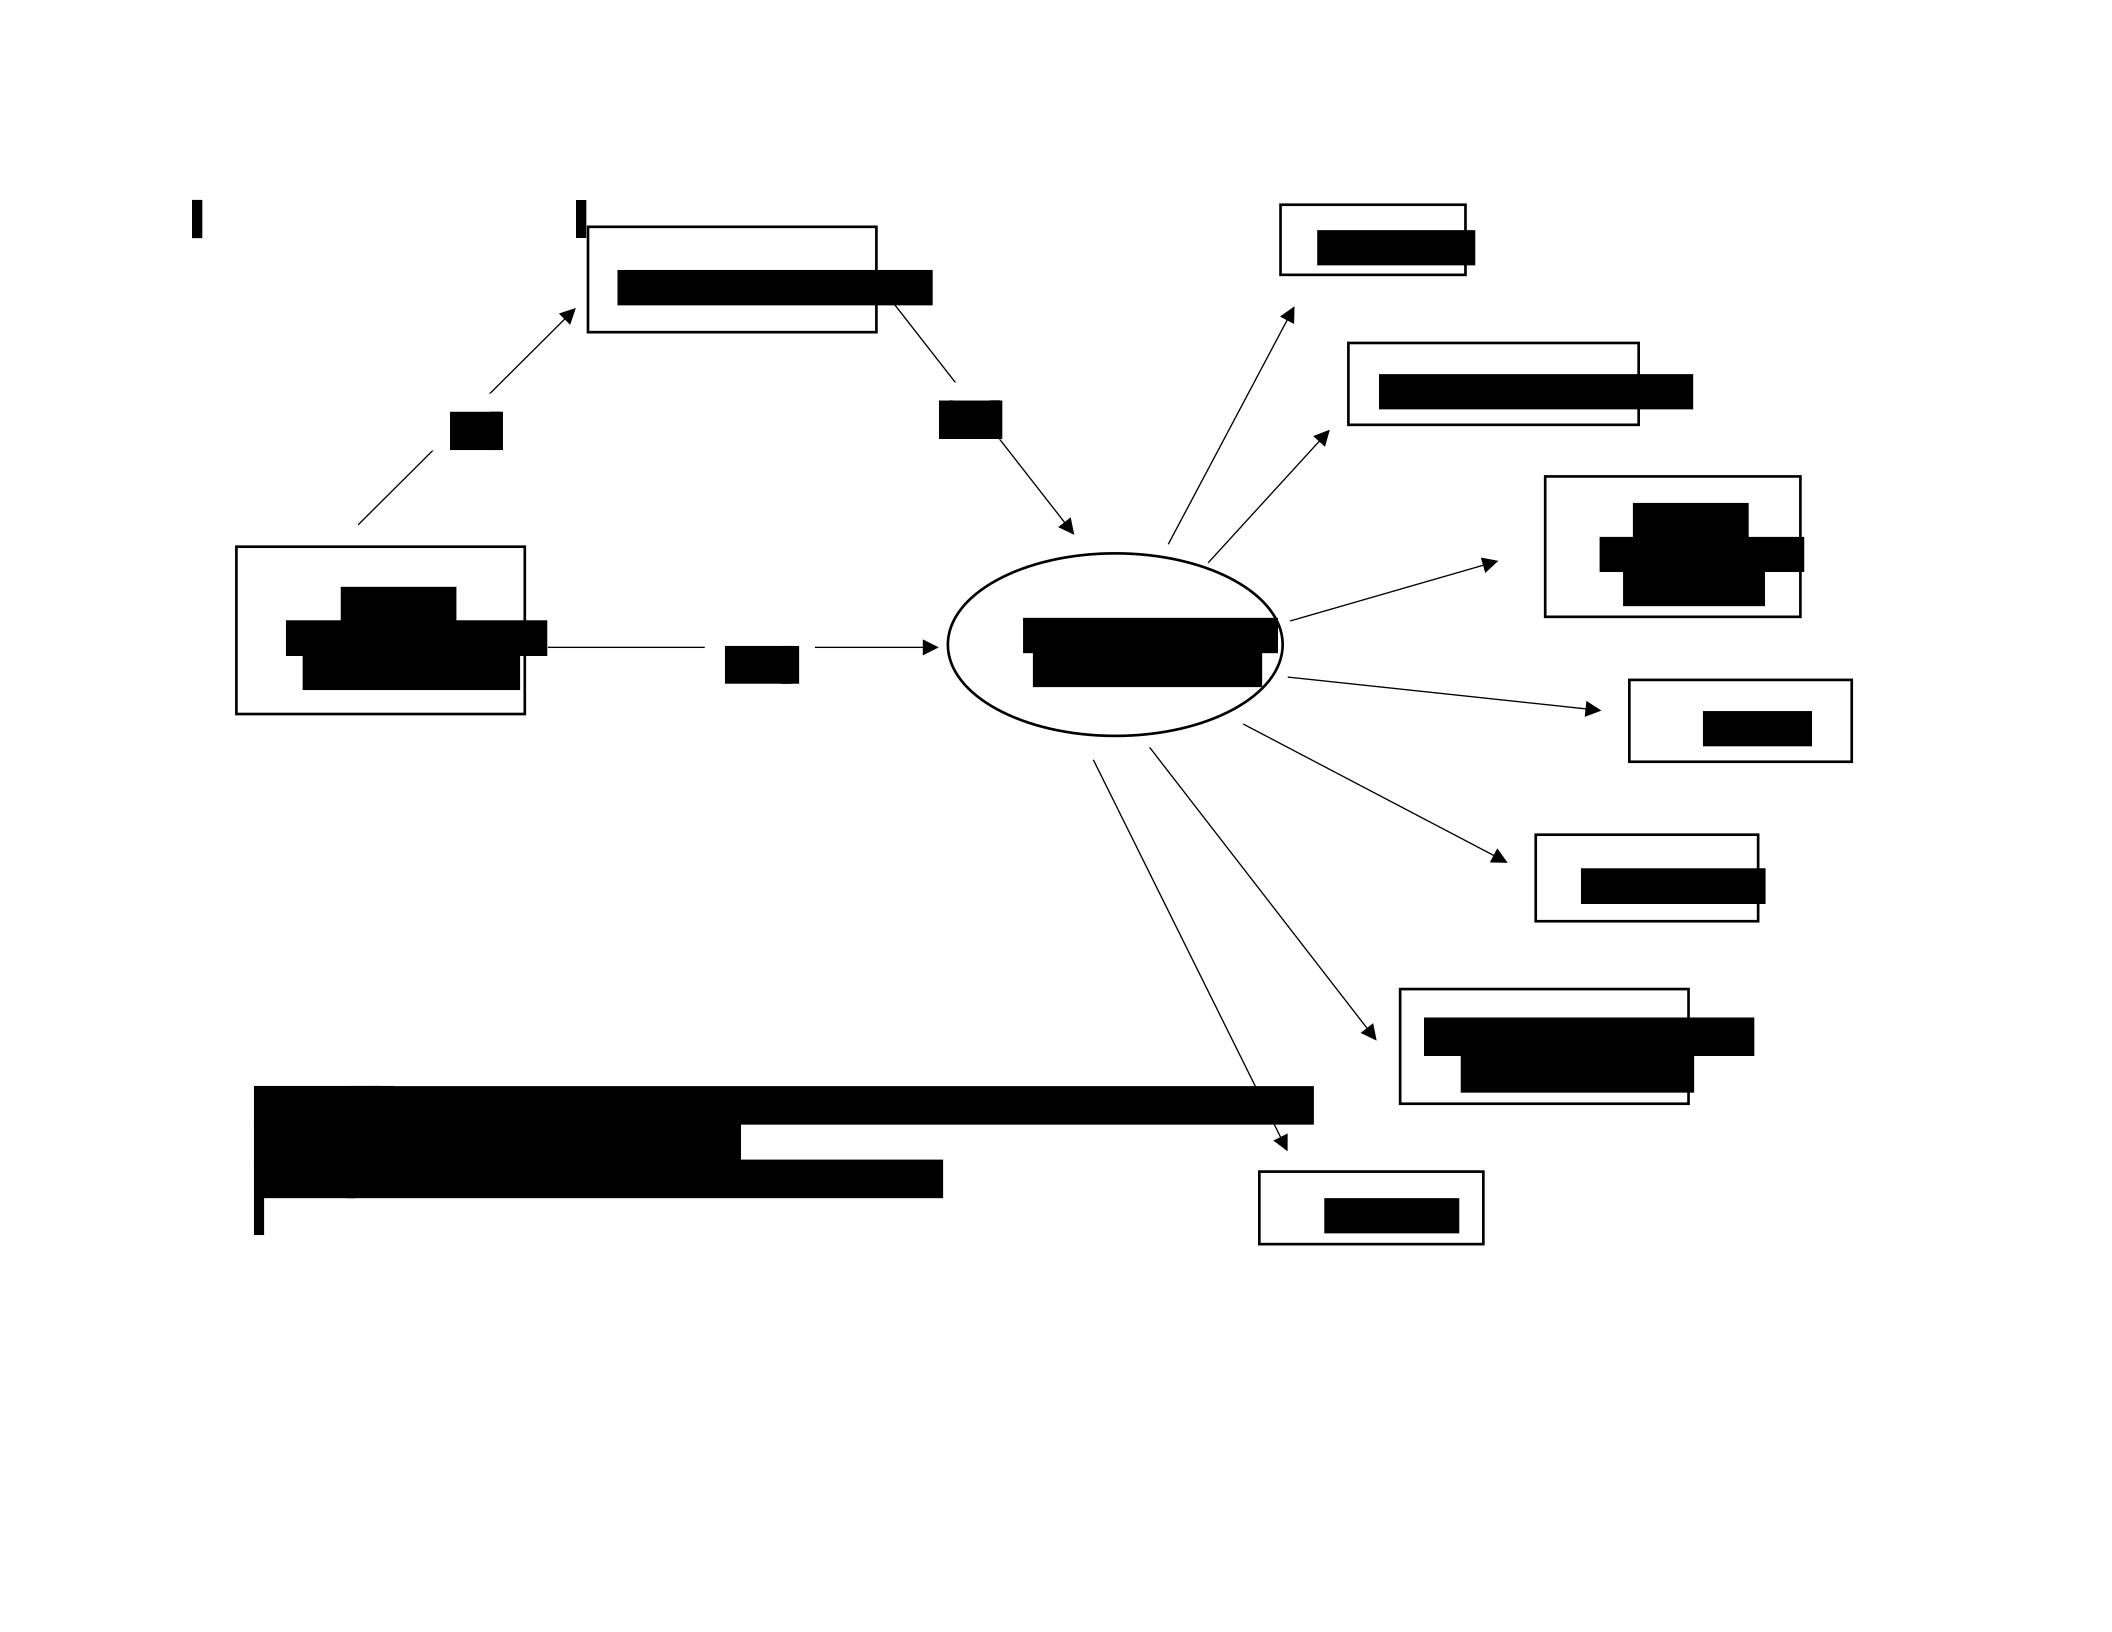
HETERONORMATIVITY AND SEXUAL HEALTH 68
Sexual
Communication
Self-Efficacy
Safe Sex Behaviors
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived physical
sexual health
Anxiety
Figure
3.
2
. Model with standardized estimates for queer women
with low heteronormativity.
Note.
*
indicates significant path, p < .05
.81*
.07
-
.19
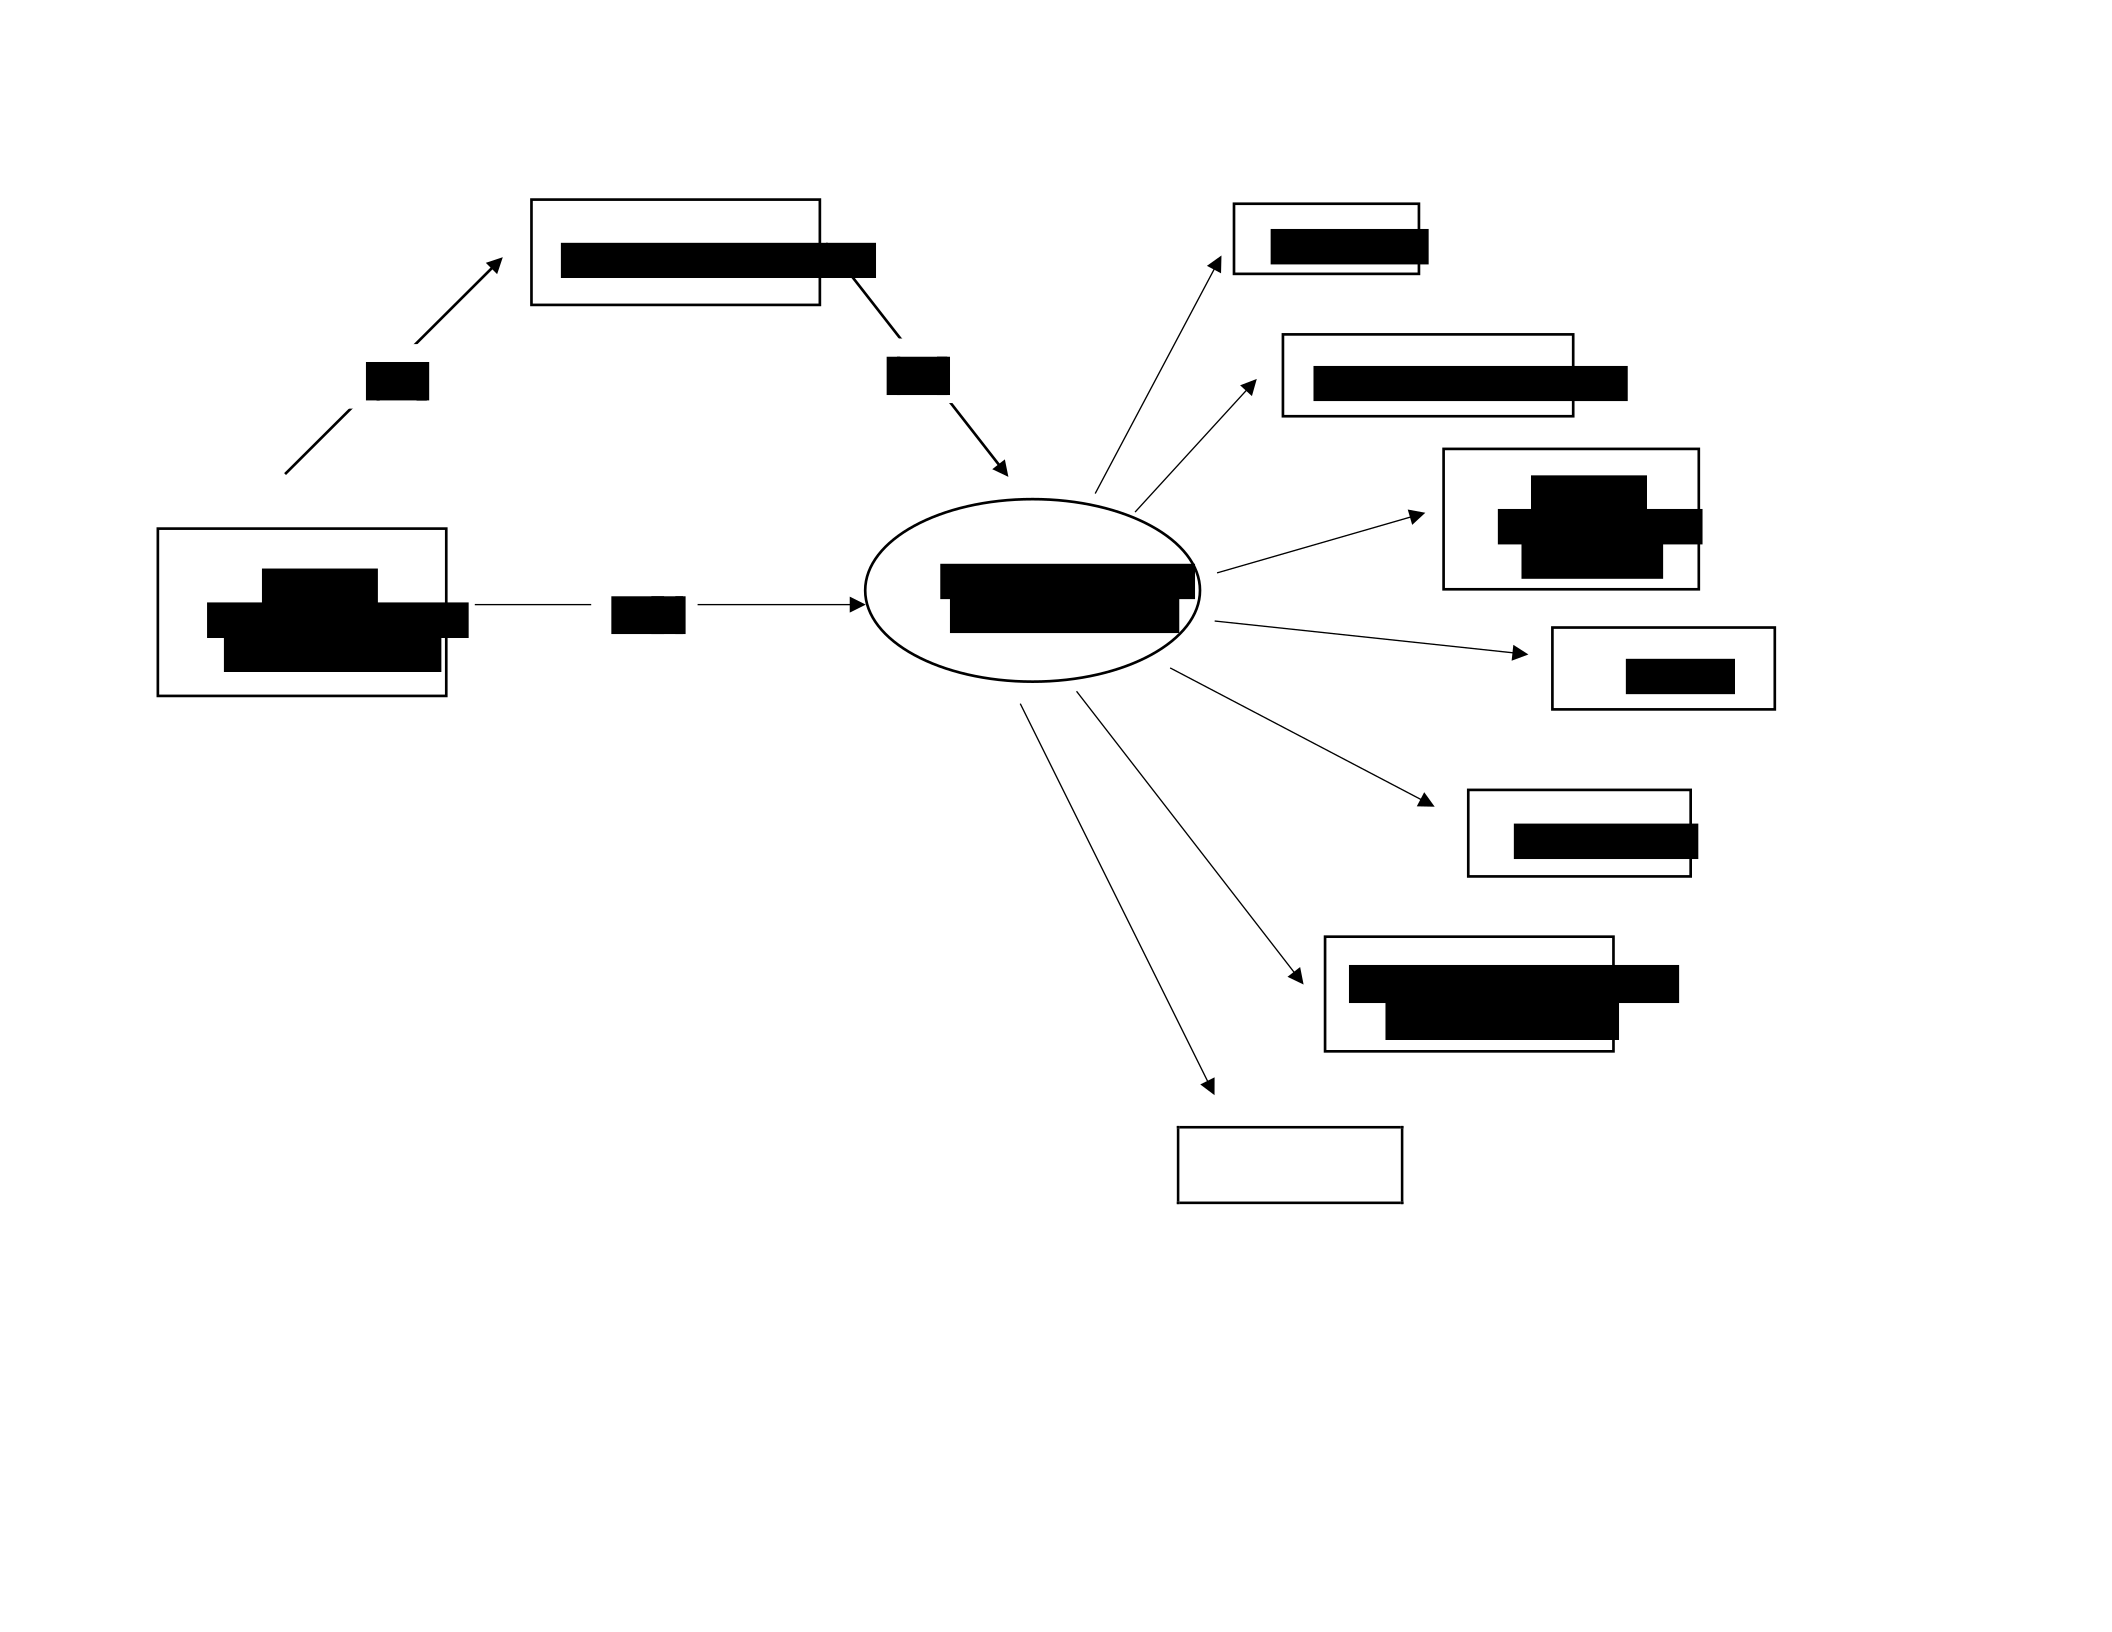
HETERONORMATIVITY AND SEXUAL HEALTH 69
Figure 3.3. Model with standardized estimates for queer women with high
heteronormativity.
Note. * indicates significant path, p < .05
Anxiety
Sexual
Communication
Self-Efficacy
Safe Sex Behaviors
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived physical
sexual health
.44
*
-
.07
-
.28

HETERONORMATIVITY AND SEXUAL HEALTH 70
CHAPTER 4: HETERONORMATIVITY, SEXUAL HEALTH COMMUNICATION,
AND COMPREHENSIVE SEXUAL HEALTH IN HETEROSEXUAL WOMEN
Sexual health has been a public health concern in recent decades (ODPHP, 2019a). The
World Health Organization (WHO; 2019) defines sexual health as “a state of physical, mental,
and social well-being in relation to sexuality” (ASHA, 2019, p.1). Unfortunately, disparities
often exist across a range of health outcomes, including those specific to sexual health.
Historically, research has frequently examined sexual health as the absence of disease (Zielinski,
2013), leading to narrow conceptualizations of sexual health and disparities (i.e., inequitable
chances of being sexually healthy based on a minority identity possessed; CDC, 2017a).
However, based on the WHO’s (2019) definition, sexual health spans more than disease and
should be examined in a more comprehensive way (Zielinski, 2013). One such group that
experiences disparities are heterosexual women. As outlined below, there appear to be sexual
health disparities present for this group across the domains described by the WHO (2019)
definition.
Heterosexual women, when compared to heterosexual men, often have poorer sexual
health outcomes (such as higher incidence of sexually transmitted infections with more severe
long-term health consequences; STIs; ODPHP, 2019a). The CDC (2019a) reported that
heterosexual women accounted for 19% of new HIV diagnoses in 2017. Of those diagnoses,
approximately 86% occurred from heterosexual contact. Conversely, best estimates suggest that
only 19% of heterosexual male HIV diagnoses occurred through heterosexual contact (CDC,
2017). The CDC (2017) also reported 1,127,651 chlamydia diagnoses in women and 577,644
chlamydia diagnoses in men. With regard to mental health, heterosexual women are more likely

HETERONORMATIVITY AND SEXUAL HEALTH 71
than heterosexual men to experience negative mental health consequences including feelings of
depression, shame, and guilt about their sexuality after engaging in sexual behavior (Allyn,
2000). Further, heterosexual women are less likely to orgasm than heterosexual men during
different-gender sexual interactions (Kinsey Institute, 2019), which has been identified as an
indicator of sexual health (WHO, 2019). Research also suggests that heterosexual women report
less autonomy in sexual decision making, such as condom use. Lower autonomy can make a
woman feel that she is not able to express her wants in the sexual encounter (Cook-Lindsay,
2013). Thus, there is substantial risk that undermine heterosexual women’s sexual health,
imploring research to examine these more closely.
ODPHP (2019) suggests that health disparities, including sexual health disparities, are an
outcome of larger social inequities. The Determinants of Health (DoH) framework, created by
the World Health Organization, proposes that health outcomes occur from a combination of
personal, social economic, and environmental factors (ODPHP, 2019). The five facets of DoH
are policymaking, social factors, health services, individual behaviors, and biology and genetics.
The role that social factors have on individual sexual health behavioral processes were examined
in this study (ODPHP, 2019).
Social factors, or social determinants of health, are the larger cultural context in which
someone exists, learns, and interacts with others (ODPHP, 2019). Social factors include cultural
norms, attitudes, social support, and social interactions. One prominent social norm in the United
States is heteronormativity (van Eeden-Moorefield, 2018). Heteronormativity is a socially
constructed, often internalized, and perpetuated belief that privileges individuals who are
heterosexual and engage in monogamous sex only in the context of legal marriage (D’Emilio &

HETERONORMATIVITY AND SEXUAL HEALTH 72
Freedman, 2012; van Eeden-Moorefield, 2018). With regard to heterosexual sexual behavior,
heteronormative scripts encourage men to be sexual aggressors and sexual decision makers,
whereas, they encourage women to be sexually chaste and ambivalent (D’Emilio & Freedman,
2012). When it comes to sexual behavior, these messages often lead to gendered power
imbalances, where women are thought to be subordinate to men (Hlavka, 2014). These
imbalances may minimize a woman’s perception of her ability to discuss her sexuality with male
partners (which is an example of an individual behavioral determinant of health, ODPHP, 2019).
This could potentially be due to fear of losing a potential sexual partner (Rinaldi-Miles, Quick,
and LaVoie, 2014) or fear of being deemed “slutty” (i.e., a woman who is presumed to be
sexually promiscuous; Armstrong, Hamilton, Armstrong & Seeley, 2014, p.104).
Importantly, the avoidance of sexual health communication has been linked to engaging
in fewer safe sex behaviors during sexual intercourse (FoSE, 2012; Widman, Noar,
ChoukasBradley, & Francis, 2014), which could result in negative sexual health outcomes.
Recent estimates suggest that only 56% of heterosexual women reported using a condom the
first time they had sex (Kinsey Institute, 2018). Additionally, in a 4 week study conducted by the
CDC (2019b), 75% of unmarried women reported never using a condom during sexual
intercourse over that span of time. This could be due, in part, to heteronormative messages
perpetuating gendered power imbalances (Rinaldi-Miles, Quick, & LaVoie, 2014). Using focus
groups, Rinaldi-Miles and colleagues (2014) found that women were likely to follow men’s
requests to not use condoms due to fear of losing a potential sexual partner. Heteronormative
scripts are patriarchal and often put men largely in charge of the sexual relationship (Lovejoy,
2015). Additionally, Rinaldi-Miles and colleagues (2014) found that men and women may share

HETERONORMATIVITY AND SEXUAL HEALTH 73
inaccurate sexual histories such that they align more closely with social norms (e.g., number of
sexual partners), which may have sexual health consequences (e.g., women saying they have
fewer sexual partners than they actually do and men saying they have more sexual partners than
they actually do to fit heteronormative scripts). Therefore, heteronormative messages may
contribute to women’s avoidance of sexual health communication and safe sex behaviors, which
may contribute to negative sexual health outcomes.
Research suggests that one way to combat these sexual health disparities is through
improving sexual health communication self-efficacy (Quinn-Nilas et al., 2016). Having high
levels of sexual communication self-efficacy (i.e., believing that you are able to discuss your
sexuality, Quinn-Nilas et al., 2016) has been linked to increased safe sex behaviors such as
improved condom use behavior (FoSE, 2012; Widman et al., 2014) as well as better overall
sexual experiences (e.g., pleasure; Jones, Robinson & Seedall, 2018). Li and Samp (2019)
examined how power was related to gender, sexual communication, and condom use in
heterosexual couples. Using an online survey, they found that women who had more power in
their relationships were more likely to use condoms and this relationship was mediated by sexual
communication. This suggests that when women felt they were able to communicate about their
sexuality, more safe sex behaviors occurred. Additionally, using dyadic path analyses of survey
data, Jones and colleagues (2018) found that sexual communication lead to higher orgasm
frequency in women and overall higher relationship satisfaction among both genders. This
further emphasizes the importance of sexual communication self-efficacy as a process to better
understand comprehensive sexual health outcomes.

HETERONORMATIVITY AND SEXUAL HEALTH 74
The Current Study
Taken together, women’s internalization of heteronormative attitudes may influence their
ability to discuss their sexuality with potential partners (Li & Samp, 2019; Rinaldi-Miles, et al.,
2014), lowering their use of safe sex behaviors (Li & Samp, 2019; Quinn-Nilas, et al., 2016),
and ultimately leading to negative comprehensive sexual health outcomes (WHO, 2019). Little
research has focused on the impact that heteronormativity has on heterosexual women’s sexual
communication self-efficacy and in turn their comprehensive sexual health outcomes. Therefore,
the purpose of this study was to examine the links between these three factors. Specifically, the
hypothesized model (see Figure 4.1) suggested a direct relationship between sexual
communication self-efficacy and comprehensive sexual health outcomes (Quinn-Nilas et al.,
2016; Widman, Choukas-Bradley, Helms, Golin & Prinstein, 2014). Because sexual
communication is often about safe sex behaviors (Widman et al., 2014), and safe sex behaviors
improve sexual health outcomes (Planned Parenthood, 2019), it was predicted that safe sex
behaviors would partially mediate this relationship. Additionally, it was predicted that
heteronormativity would moderate the entire model (see Figure 4.2). Women may avoid
discussing their sexuality with a potential partner because heteronormativity encourages women
to stay silent about their sexuality (D’Emilio & Freedman, 2012). Further, heterosexual women
may accept male condom use preferences (because of heteronormative scripts), and therefore,
engage in fewer safe sex behaviors leading to negative sexual health outcomes (Rinaldi-Miles et
al., 2014). Finally, it was predicted that heteronormativity would moderate the direct relationship
between sexual communication self-efficacy and comprehensive sexual health outcomes.
Women may feel that discussing their sexuality will lead to social and relationship repercussions

HETERONORMATIVITY AND SEXUAL HEALTH 75
and therefore, may choose not to discuss her sexual health. This in turn, would lead to more
negative sexual health outcomes (Cunningham, Tschann, Gurvey, Fortenberry & Ellen, 2002;
D’Emilio & Freedman, 2012).
Methods
Sample
Data were collected from a convenience sample of 188 cisgender heterosexual women
from across the United States who were surveyed online through Facebook (which meets power
needs for the analysis, .90; G*Power). Participant ages ranged from 19 to 82 (M = 34, SD =
11.14). The overwhelming majority of the sample was Non-Hispanic White women (88.80%).
Additionally, the sample was highly educated: 41.50% reported earning a bachelor’s degree,
followed by 28.70% reported earning a master’s degree, and 12.80% reported earning an
advanced graduate degree (e.g., PhD, MD, DO). Additionally, almost all participants (97.90%)
reported having health insurance at the time they participated in the survey. More than half (i.e.,
61.00%) of the participants made over $75,000 a year (Table 4.1).
Procedure
The research team posted a recruitment announcement (Appendix A) to their personal
Facebook pages that informed people about the online 30-minute study about sexual health. The
announcement included a link to the informed consent (Appendix B) and survey (Appendix C).
The announcement also asked followers to share information about the study on their own pages
(i.e., snowball sampling; Gelinas et al., 2017). Recruitment through social media has become a
popular strategy to identify participants because of its widespread use, ease of dissemination,
and ability to reach diverse and hard to reach populations (Urban & van Eeden-Moorefield,
2018; Gelinas et al., 2017). At the end of the survey participants were given the option to

HETERONORMATIVITY AND SEXUAL HEALTH 76
participate in a raffle to receive one of 40 $25 Amazon gift cards (Appendix D). Information for
the raffle was input into an unlinked page so that participant responses remained anonymous
(Appendix E).
The survey was set so that it could only be taken one time per each IP address to safeguard data
independence (Birnbaum, 2004).
Measures
The survey consisted of demographic questions (e.g., age, race, ethnicity, SES) as well as
those that asked participants about their sexual health communication self-efficacy, safe sex
behaviors, internalized heteronormativity, and comprehensive sexual health over the last 12
months. The CDC (2017a, 2017b, 2017c) recommends that individuals get tested for STIs and
HIV once every 12 months to assess their sexual health. Therefore, participants were asked to
reflect on their experiences over that time span. Some scales (i.e., Heteronormativity, Anxiety,
Depression, Sexual Functioning; originally a dysfunction scale, and STIs) were reverse scored so
that higher scores indicated better sexual health. For example, in the heteronormativity measure,
high scores indicated lower heteronormative attitudes and lower scores indicated higher
heteronormative attitudes. Although this might seem counterintuitive, we wanted all higher
scores to reflect a more positive dimension of the variables measured (e.g., a lower
heteronormative attitude is good and related to more positive outcomes; Habarth, Holmes,
Sandoval, & Balsam, 2019). Table 4.2 presents scale descriptive statistics (i.e., minimum,
maximum, mean, standard deviation, and reliability).
Sexual communication self-efficacy. A revised 15-item version of the Quinn-Nilas and
colleagues (2016) sexual communication self-efficacy scale was used to measure participants’

HETERONORMATIVITY AND SEXUAL HEALTH 77
perceptions of their ability to discuss their sexuality with a partner. Participants rated their
perceived ability to engage in 15 conversations with a sexual partner using a 4-point Likert scale
(1= very difficult to 4= very easy). Sample items included: “Tell them you would like to have
sex more often?” and “Tell them a sexual activity feels good.” Scores were summed and higher
scores indicated higher sexual communication self-efficacy.
Safe sex behaviors. Due to length, DiIorio’s (2009) Safe Sex Behavior Questionnaire
was modified to 8 questions and used to measure safe sex behavior. Questions that were specific
to the sexual health indicators used in this study were included. Sample questions include “I
stop foreplay long enough to put on a condom (or for my partner to put on a condom)” and “I
ask potential partners about their sexual histories” (1=never to 4= always). Two questions were
reverse scored. Scores were summed and higher scores indicated more safe sex behaviors.
Heteronormativity. Habarth’s (2014) Heteronormative Attitudes and Beliefs scale was
used to measure heteronormativity. This scale consisted of two subscales: Essential Sex and
Gender Subscale and the Normative Behavior Subscale. Together, this scale consisted of 16
items measured on a likert scale (1= strongly disagree, 7= strongly agree). Sample questions
included: “People who say that there are only two legitimate genders are mistaken”. Eight
questions were reverse scored. Items were summed.
Comprehensive sexual health. Comprehensive sexual health was measured as a latent
variable using the WHO (2019) comprehensive definition of sexual health. The observed
variables were anxiety, depression, perceived physical sexual health, safety, sexual functioning,
sexual satisfaction/pleasure, and STIs/HIV.

HETERONORMATIVITY AND SEXUAL HEALTH 78
Anxiety. With reference to Janda & O’Grady’s (1980) Sex Anxiety Inventory, an author
created 3-item scale was used to measure sexual anxiety. “I generally feel anxious about
masturbation” was a sample question and was measured using a 7-point Likert scale (1= Not
true of me at all, 7= Very true of me). Scores were then summed. The scale was reverse coded so
that higher scores indicated lower sexual anxiety.
Depression. A modified version of Radloff’s (1977) 12-item CESD-R was used to
measure depressive symptoms. This 10-item summed scale asked participants to indicate the
number of times they felt or behaved in a certain way in the last week. Responses were measured
on a 4-point Likert Scale (1= rarely or none of the time; less than 1 day, 4= most or all of the
time; 5-7 days). An example question was: “I had trouble keeping my mind on what I was
doing.”
Perceived physical sexual health. Author(s) created an item to measure global perceived
physical sexual health. The question asked, “To what extent do you feel you are physically
healthy enough to have sex?” and used a likert scale (1= Not at all healthy, 4=Very healthy).
Safety. Author(s) created an item to measure global perceived safety in sexual
encounters. The question asked “Think about the last time you engaged in sex with a partner.
How safe did you feel?” (1= Not safe at all, 5=Very safe).
Sexual functioning. A 5-item modified version of Rosen’s (2000) Female Sexual
Function Index was used to asses female sexual functioning (i.e., desire, arousal, lubrication,
orgasm, and pain). A sample question was “How often did you find it difficult to have an orgasm
when you wanted to?” (1= never, 7= always).

HETERONORMATIVITY AND SEXUAL HEALTH 79
Sexual Satisfaction/Pleasure. A version of the summed Male Sexual Health
Questionnaire (Rosen et al., 2004) was modified to apply to women and was used to measure
experiences of sexual satisfaction and pleasure. Questions were asked without assuming the
gender of the participant. “How satisfied are you with the quality of the sex life you have?” was
an example question and was measured on a 5-point Likert scale (1= Not at all satisfied, 5=
Very satisfied). Higher scores indicated more sexual satisfaction and pleasure.
STIs/HIV. Author created questions were used to assess participant experiences with
STIs and HIV. Questions assessed frequency of STI and HIV testing and number of Chlamydia,
Gonorrhea, and/or Syphilis diagnoses over the last year. Because herpes and HIV are treatable
chronic conditions, two single-item measures were used to identify if participants had herpes or
HIV. The questions asked, “Do you have herpes?” and “Do you have HIV?” Answers included
“yes, no, not sure, prefer not to answer.” In this sample, no women responded that they were
HIV positive and therefore, HIV was excluded from scale combination. For score combination,
herpes was recoded so that so that yes=1 and no =0. Then all STI scores were combined and
scores ranged from three to six.
Data Analysis Plan
Data were imported into SPSS for cleaning and assessment of normality, reliability, and
missingness. Scores were summed and preliminary relationships between variables were
analyzed and were as expected (see Table 4.3). Once cleaned, data were imported into AMOS for
analysis and model testing was conducted sequentially. First, to ensure fit of the measurement
model (i.e., the observed variables used to measure the latent construct of comprehensive sexual
health outcomes), a confirmatory factor analysis (CFA) was conducted using maximum

HETERONORMATIVITY AND SEXUAL HEALTH 80
likelihood estimation (Schumacker & Lomax, 2010). Model fit was assessed using Chi Square
(χ2) test, RMSEA, CFI, and SRMR (Schumacker & Lomax, 2010).
AMOS was used to test the hypothesized moderated-mediation model (Arbuckle, 2013)
using ML estimation because of its ability to predict robust parameters for a mix of observed and
latent variables (Schumacker & Lomax, 2010). To test for mediation, 1,000 bootstraps were run.
Bootstrapping takes random subsamples and estimates them to see if they are likely present in
the model (Cheong & MacKinnon, 2012). To test for moderation of the model, first a median
split was used to identify groups that had high internalized heteronormativity and low
internalized heteronormativity. Then a multi-group analysis was run in AMOS (Arbuckle, 2013)
which compared both the constrained (or theoretically predicted) and unconstrained (estimated
models).
Results
Preliminary Results
Correlations were used to assess the need to include controls in the model. A number of
demographic variables were correlated with at least one observed endogenous variable.
Specifically, education was correlated with sexual functioning (r(186) = -.18, p < .05), income
was significantly correlated with STIs (r(186) = .18, p< .05), depression (r(186) = .16, p < .05),
anxiety (r(186) = .24, p < .05), and feelings of safety (r(186) = .18, p < .05). Finally, health
insurance was related to sexual functioning (r(186) = .18, p < .05). However, when added to the
model, no controls were significant. Therefore, they were all dropped from the model.
Missing data analysis was conducted using SPSS’s Missing Value analysis. No variable
had more than 20% missing responses, suggesting responses were missing completely at random

HETERONORMATIVITY AND SEXUAL HEALTH 81
(Dong & Peng, 2013). Missing data were replaced using five estimation rounds of multiple
imputation (MI) in SPSS. MI is reliable with replacing missing data of varying sizes and is very
efficient (Madley-Dowd, Hughes, Tilling, & Heron, 2019). A CFA was conducted to validate
measurement of the latent construct of sexual health. Model fit was strong and all parameter
estimates were significant except STI diagnoses (See Chapter 2). As stated in the measurement
section, scores were coded so that higher scores indicated higher sexual health. This was to
ensure consistency within the latent measurement.
Hypothesized Model Testing
First, the base mediation model was tested. This model tested the direct relationship
between sexual communication self-efficacy and comprehensive sexual health outcomes as well
as the indirect relationship through safe sex behaviors. Results suggested the model had good fit,
χ2(21, N=188)=27.39, p = .16, CFI = 0.98, GFI = .97, RMSEA = .04, and accounted for 65% of
the variation in comprehensive sexual health. All parameter estimates were significant except the
link between sexual communication self-efficacy and safe sex behaviors (p = .06, See Table 4.4,
Figure 4.1). Therefore, the indirect effect was not significant for the full model. However, there
was a moderately strong negative relationship between safe sex behaviors and comprehensive
sexual health outcomes in this model. In other words, as safe sex behaviors increased,
comprehensive sexual health outcomes decreased. That is, as women used more safe sex
behaviors they experienced decreases in their comprehensive sexual health. Notably, results
suggest a strong direct positive relationship between sexual communication self-efficacy and
comprehensive sexual health outcomes. Thus, the base mediation model fit the data which

HETERONORMATIVITY AND SEXUAL HEALTH 82
suggested the presence of at least partial mediation might be found in the full moderated
mediation model.
Therefore, using multi-group analysis, moderation of the mediation model was tested.
Groups were heterosexual women with high internalized heteronormativity and heterosexual
women with low internalized heteronormativity. Results suggested that moderation was present
at the model level. Of additional interest, the model for women with high internalized
heteronormativity only accounted for 57% of the variation in comprehensive sexual health
outcomes (R2=.57), which is less than the variance explained by the base mediation model.
Contrastingly, the model for women with low internalized heteronormativity accounted for 73%
of the variance in comprehensive sexual health (R2=.73).
Further probing of model links was conducted using The Stats Tool Package excel file
(Gaskin, 2012) to identify which links demonstrated moderation. First, the direct link between
sexual communication self-efficacy and comprehensive sexual health was tested, and there was
not significant moderation (i.e., χ2(43, N =188) = 47.66 < 48.44 which was the 90% CI
threshold). Note, both groups demonstrated strong direct links though. Next, the link between
sexual communication self-efficacy and safe sex behaviors was tested for moderation.
Moderation was present with the link being significant (p < .05) for women who had high
internalized heteronormativity (see Figure 4.2), but insignificant for women who had low
internalized heteronormativity (see Figure 4.3; χ2(43, N = 188) = 48.55 > 48.44 which was the
90% CI threshold). We then tested the second part of the indirect effect pathway: the link
between safe sex behaviors and comprehensive sexual health outcomes. This link was not
significantly moderated, but remained significant for both groups (χ2(43, N = 188) = 46.70 <

HETERONORMATIVITY AND SEXUAL HEALTH 83
48.44 which was the 90% CI threshold). Taken together, partial moderation of the mediation
model was only present for women with high internalized heteronormativity.
Discussion
Grounded in a DoH framework, this study examined the links between sexual
communication self-efficacy, safe sex behaviors, and comprehensive sexual health outcomes,
within the context of heteronormativity among cisgender heterosexual women. The hypothesized
model predicted that sexual communication self-efficacy would predict comprehensive sexual
health, and that this link would be partially mediated by safe sex behaviors and moderated by
heteronormativity. Data partially support our moderated mediation hypothesis: Partial mediation
was only present for heterosexual women with high internalized heteronormativity. In other
words, the link between communication self-efficacy and comprehensive sexual health outcomes
acted differently for women with high internalized heteronormativity and women with low
internalized heteronormativity. However, the link between safe sex behaviors and comprehensive
sexual health outcomes and the direct relationship between sexual communication self-efficacy
and comprehensive sexual health outcomes did not significantly change. Therefore, although
data did not completely support the hypothesized model, these findings make significant
contributions to the literature. These are discussed below.
First, the direct relationship between sexual communication self-efficacy and
comprehensive sexual health outcomes stayed strong, positive, and significant for heterosexual
women regardless of their level of internalized heteronormativity. This is consistent with the
previous research that sexual communication self-efficacy contributes to better sexual health
outcomes (e.g., Widman et al., 2014). For example, Landor and Winter (2019) wanted to

HETERONORMATIVITY AND SEXUAL HEALTH 84
understand how relationship quality, comfort with sexual communication, and safe sex outcomes
are related for young women in monogamous relationships. They found that relationship quality
and being comfortable communicating about sex was associated to pregnancy prevention (i.e.,
through condom use and contraceptive use) and substance use during sexual encounters. Those
who were comfortable communicating about sex with a partner took more precautions during
sexual intercourse. Thus, supporting that women with high sexual communication self-efficacy
have better comprehensive sexual health.
Moderation of the indirect effect partially supported our hypothesized model.
Specifically, the indirect effect was only significant for heterosexual women with high
internalized heteronormativity. For women with low internalized heteronormativity, this path
remained insignificant with a low parameter estimate, suggesting that this relationship did not
exist for this group. Culturally, women are taught that they should not speak about sex or be
sexually knowledgeable about their bodies (D’Emilio & Freedman, 2012). For example, women
understanding what behaviors may lead to sexual pleasure and orgasm (e.g., through solo
masturbation) may result in women being slut shamed (D’Emilio & Freedman, 2012; Haus &
Thompson, 2019), perpetuating the sexual double standard that men should be sexual but women
should not (Haus & Thompson, 2019). Using grounded theory methodology, Kaestle and Allen
(2011) examined college student perceptions of masturbation. They asked questions about how
they learned about masturbation, how they internalized social stigma and taboos related to
masturbation, and how they navigated the relationship between stigma and pleasure. They found
that most students believed that masturbation was more acceptable for men than women, and
they were apprehensive to even discuss masturbation. Men discussed masturbation as a positive

HETERONORMATIVITY AND SEXUAL HEALTH 85
and healthy behavior, whereas women were less descriptive and positive about their experiences.
This demonstrated the pervasiveness of culturally stigmatizing scripts for women and their
sexuality. Thus, women with high internalized heteronormativity may not believe that they
should talk about the numerous facets of sexual health (e.g., sexual pleasure, sexual history,
sexual concerns; Horan, 2016; Lehmiller, et al., 2014) out of fear they may be viewed as a slut or
be shamed by a partner (e.g., sexual double standard; Greene, & Faulkner 2005).
However, for heterosexual women with high internalized heteronormativity, discussing
safe sex behaviors may be less threatening, and therefore, their sexual communication focuses on
those. The discussion of safe sex behaviors, within heterosexual relationships, is commonly
discussed in school sexuality education (Baptiste-Roberts, 2017), the media (Martino, Collins,
Kanouse, Elliot, & Berry, 2005), and by parents (Widman, Choukas-Bradley, Noar, & Garrett,
2016). Therefore, heterosexual women who have high heteronormativity may still feel
comfortable discussing safe sex behaviors with a partner, since that is somewhat normalized in
society. For women who have low internalized heteronormativity, perhaps they do not prescribe
to the cultural norms that have perpetuated shame and silence around women communicating
about their sexuality. This group of women may have more self-efficacy in discussing other
facets of sexual health with a partner, and therefore, indirect discussions of sexuality through
safe sex behaviors does not exist.
Finally, for both models, the relationship between safe sex behaviors and comprehensive
sexual health outcomes was negative and significant (i.e., safe sex behaviors decreased,
comprehensive sexual health outcomes increased). These findings were not consistent with our
hypothesis; however, they suggest that engaging in safe sex behaviors for heterosexual women

HETERONORMATIVITY AND SEXUAL HEALTH 86
may not lead to better comprehensive sexual health. First this could be due to error in
measurement of STIs, which would be the most directly affected indicator of engaging in safe
sex behaviors (e.g., CDC, 2013). If STIs were measured differently leading to a significant factor
loading on comprehensive sexual health, it is possible that this relationship would change to
positive. However, it is possible that these findings are a function of gendered power
differentials that often occur in heterosexual sexual intercourse (Hlavka, 2014). For example,
condom use negotiation can be a gendered and power-based. Men may prefer to have
unprotected intercourse due to decreased sensation when using a condom (Grady, et al., 1993).
So, when a woman suggests her preference to use condoms during sex her partner may
encourage her not to in order to improve his sexual experience (Conley & Collins, 2006; Grady,
Klepinger, Billy, & Tanfer, 1993). Women may agree to this, out of fear of losing the romantic
partner in the long run
(Rinaldi-Miles et al., 2014). Therefore, even though women feel that they are able to talk about
safe sex behaviors, male dominated sexual scripts override that self-efficacy. Additionally,
women may now have higher feelings of anxiety, depression, and lower feelings of safety, since
their preferences were ignored, resulting in lower comprehensive sexual health outcomes.
Additionally, this model explained less of the variance across comprehensive sexual health than
the base mediation model. This suggests that there may be other variables that influence
comprehensive sexual health outcomes that were not presented in the original model for this
group. Based on the previous explanation, perhaps more variance would be explained for women
with high heteronormativity, if the model included partner communication and partner safe sex
behavior preferences. The decision to engage in safe sex behaviors is more of a dyadic

HETERONORMATIVITY AND SEXUAL HEALTH 87
interpersonal process, and therefore, understanding both partners preferences may enhance the
model.
Conclusion
Notably, the extant literature has focused almost exclusively on behavioral and individual
indicators of sexual health (i.e., safe sex behaviors prevent STIs), which has overlooked how
individual and cultural processes interact, which can directly predict comprehensive sexual
health outcomes (Schalet, 2011). Results from the current study suggested that communication
self-efficacy is the strongest predictor of comprehensive sexual health for heterosexual women
and that the indirect relationship of sexual communication self-efficacy, safe sex behaviors, and
comprehensive sexual health outcomes is only present in women with high internalized
heteronormativity. Thus, when studying heterosexual women’s comprehensive sexual health,
research must consider cultural context and the impact of heteronormative gendered power
differentials and shaming women’s sexuality.
Limitations
Our results must be considered within the limitations of our study. First, research
suggests that when discussing sex, sexual behaviors, and sexual health, participants may respond
in socially desirable ways or untruthful ways to avoid disclosing potentially stigmatizing
information (Schroder, Carey & Vanable, 2003). Therefore, it is important to consider the
accuracy of the self-reports (Schroder et al., 2003). Using online surveys has been found to
alleviate some of the limitations that are present when surveying about sexuality, because of
enhanced anonymity (Schroder et al., 2003). Therefore, online survey methodology was selected
for this reason. However, online surveys comes with shortcomings of their own (Lefever, Dal, &

HETERONORMATIVITY AND SEXUAL HEALTH 88
Matthaisdottir, 2007). For example, the researcher cannot confirm that participants fit the
inclusion criteria to participate in the study (Lefver et al., 2007). To combat this, recruiting
through social media networks (such as Facebook) can provide more assurance that participants
fit search criteria. Additionally, this provides easy access to a population from which to collect
data (King, O’Rourke, & DeLongis, 2014). One limitation of recruiting through social media,
that was evident in this study, is the collection of homogenous samples (King et al., 2014). In
theory, people from diverse backgrounds are on social media and therefore, it is a tool to access
diverse samples (King et al., 2014). However, when recruiting through personal friend networks,
it is likely that samples will be somewhat homogenous given people tend to be friends with
people that are similar to them (Naruchitparames, Gunes, & Louis, 2011). Accordingly, it makes
sense that our sample was homogenous and socially privileged (e.g., mostly White, middleclass).
Additionally, our study was cross-sectional. Both of these factors combined suggest that our
results must be considered within the confines of our study. However, as outlined in the
discussion, enough research exists that supports our findings, which would suggest that similar
results may be seen across more diverse populations. That being said, future research should use
these models with more diverse populations, to understand how sexual communication
selfefficacy, safe sex behaviors, and comprehensive sexual health outcomes interact across
diverse groups.

HETERONORMATIVITY AND SEXUAL HEALTH 89
References
Allyn, D. (2000). Make love, not war. The sexual revolution: An unfetted history. New York,
United States: Little, Brown and Company.
Arbuckle, J. L. (2013). Amos 22 user’s guide. Chicago, IL: SPSS.
Armstrong, E. A., Hamilton, L. T., Armstrong, E. M., & Seeley, J. L. (2014). “Good girls”:
Gender, social class, and slut discourse on campus. Social Psychology Quarterly, 77(2),
100-122. doi: 10.1177/0190272514521220
ASHA. (2019). Understanding sexual health. Retrieved on May 12, 2019 from
http://www.ashasexualhealth.org/sexual-health/
Baptiste-Roberts, K., Oranuba, E., Werts, N., & Edwards, L. V. (2017). Addressing healthcare
disparities among sexual minorities. Obstetrics and Gynecology Clinics of North
America, 44, 71-80. doi: 10.1016/j.ogc.2016.11.003
Birnbaum, M. H. (2004). Human research and data collection via the internet. Annual Review of
Psychology, 55, 803-832. doi: 10.1146/annurev.psych.55.090902.141601
Byrne, B. M. (2010). Structural equation modeling with AMOS: Basic concepts, applications,
and programming (3rd ed.). New York, United States: Routledge Taylor & Francis
Group.
CDC. (2013). Condom fact sheet in brief. Retrieved from
https://www.cdc.gov/condomeffectiveness/brief.html
CDC. (2017a). STD health equity. Retrieved on May 12, 2019 from
https://www.cdc.gov/std/health-disparities/default.htm

HETERONORMATIVITY AND SEXUAL HEALTH 90
CDC. (2017b). HIV among men in the United States. Retrieved on May 11, 2019 from
https://www.cdc.gov/hiv/group/gender/men/index.html
CDC. (2017c). Sexually Transmitted Disease Surveillance 2017. Chlamydia. Retrieved on April
19, 2020 from https://www.cdc.gov/std/stats17/chlamydia.htm
CDC. (2019a). HIV among women. Retrieved on May 3, 2019 from
https://www.cdc.gov/hiv/group/gender/women/
CDC. (2019b). Key statistics from the national survey of family growth- C listing. National
Center for Health Statistics. Retrieved on June 10, 2019 from
https://www.cdc.gov/nchs/nsfg/key_statistics/c.htm#consistencycondom
Cheong, J., & MacKinnon, D. P. (2012). Mediation/ indirect effects in structural equation
modeling. In R. H. Hoyle (Ed.), Handbook of Structural Equation Modeling (pp. 425-
436). New York, United States: The Guildford Press.
Conley, T. D., & Collins, B. E. (2006). Differences between condom users and condom nonusers
in their multidimensional condom attitudes. Journal of Applied Psychology, 35(3), 603-
620. doi: 10.1111/j.1559-1816.2005.tb02137.x
Cook-Lindsay, B. A. (2013). Gender-based power imbalances and condom-use negotiations. The
Health Education Monograph Series, 30(2), 28-33. doi: 10.1177/0017896912450240
Cunningham, S. D., Tschann, J., Gurvey, J. E., Fortenberry, J. D., & Ellen, J. M. (2002).
Attitudes about sexual disclosure and perceptions of stigma and shame. Journal of
Journal of Sexually Transmitted Infections, 78, 334-338.
https://doi.org/10.1136/sti.78.5.334
D’Emilio, J. D., & Freedman, E. B. (2012). Intimate matters: A history of sexuality. (3ed).

HETERONORMATIVITY AND SEXUAL HEALTH 91
Chicago, United States: The University of Chicago Press.
DiIorio, C. (2009). Safe sex behavior questionnaire. In T. D. Fisher, C. M. Davis, W. L. Yarber,
& S. L. Davis (Eds.), Handbook of sexuality-related measures (pp.594-596). New York,
NY: Routledge.
Dong, Y., & Peng, C. J. (2013). Principled missing data methods for researchers. Springerplus,
2, 222. doi: 10.1186/2193-1801-2-222
Future of Sex Education Initiative. [FoSE]. (2012). National sexuality education standards: Core
content and kills, K-12 [a special publication of the Journal of School Health]. Retrieved
on April 19, 2020 from http://www.futureofsexeducation. org/documents/josh-
fosestandards-web.pdf
Gaskin, J. (2012). The Stats Tools Package. [excel file]
Gelinas, L., Pierce, R., Cohen, I. G., Lynch, H. F., & Bierer, B. E. (2017). Using social media as
a research recruitment tool: Ethical issues and recommendations. The American Journal
of Bioethics, 17(3), 3-14. doi: 10.1080/15265161.2016.1276644
Grady, W. R., Klepinger, D. H., Billy, J. O., & Tanfer, K. (1993). Condom characteristics: The
perceptions and preferences of men in the United States. Family Planning Perspective,
25(2), 67-73. doi: 10.2307/2136208
Greene, K., & Faulkner S. L. (2005). Gender, beliefs in sexual double standard, and sexual talk
in heterosexual dating relationships. Sex Roles, 53(3/4). doi: 10.1007/s11199-005-5682-6
Habarth, J. M. (2014). Development of the heteronormative attitudes and beliefs scale.
Psychology & Sexuality, 1-24. doi: 10.1080/19419899.2013.876444
Habarth, J. M., Wickham, R. E., Holmes, K. M., Sandoval, M., & Balsam, K. F. (2019).
Heteronormativity and women’s psychosocial functioning in heterosexual and same-sex

HETERONORMATIVITY AND SEXUAL HEALTH 92
couples. Psychology & Sexuality, 10(3), 185-199. doi:
https://doi.org/10.1080/19419899.2019.1578994
Haus, K. R., & Thompson, A. E., (2019). An examination of the sexual double standard
pertaining to masturbation and the impact of assumed motives. Sexuality & Culture.
https://doi.org/10.1007/s12119-019-09666-8
Hlavka, H. R. (2014). Normalizing sexual violence: Young women account for harassment and
abuse. Gender and Society, 28(3), 337-358. doi: 10.1177/0891243214526468
Horan, S. M. (2016). Further understanding sexual communication: Honesty, deception, safety,
and risk. Journal of Social and Personal Relationships, 33(4), 449-468. doi:
10.1177/0265407515578821
Janda, L. H. & O’Grady, K. E. (1980). Development of a sex anxiety inventory. Journal of
Consulting and Clinical Psychology, 48, 169-175. doi: 10.1037/t02581-000
Jones, A. C., Robinson, W. D., & Seedall, R. B. (2018). The role of sexual communication in
couples’ sexual outcomes: A dyadic path analysis. Journal of Marital and Family
Therapy, 44(4), 606-623. doi: 10.1111/jmft.12282
Kaestle, C. E., & Allen, K. R. (2011). The role of masturbation in healthy sexual development:
Perceptions of young adults. Archives of Sexual Behavior, 40, 983-994. doi: 4 DOI
10.1007/s10508-010-9722-0
King, D. B., O’Rourke, N., & DeLongis, A. (2014). Social media recruitment and online data
collection: A beginner’s guide and best practices for accessing low-prevalence and
hardto-reach populations. Canadian Psychology, 53(4), 240-249. doi:
10.1037%2Fa0038087

HETERONORMATIVITY AND SEXUAL HEALTH 93
Kinsey Institute. (2018). FAQs & sex information. Retrieved on May 29, 2019 from
https://kinseyinstitute.org/research/faq.php
Kinsey Institute. (2019). FAQs & sex information. Retrieved on May 29, 2019 from
https://kinseyinstitute.org/research/faq.php
Landor, A. M., & Winter, V. R. (2019). Relationship quality and comfort talking about sex as
predictors of sexual health among young women. Journal of Social and Personal Relationships,
36(11-12) 3934-3959. doi: https://doi.org/10.1177/0265407519842337 Lefever, S., Dal, M., &
Matthiasdottir, A. (2007). Online data collection in academic research: Advantages and
limitations. British Journal of Educational Technology, 38(4), 574-582. doi:10.1111/j.1467-
8535.2006.00638.x
Lefkowitz, E., Shearer, C. L., Gillen, M. M., & Espinosa-Hernandez, G. (2014). How gendered
attitudes related to women’s and men’s sexual behaviors and beliefs. Sexuality and
Culture, 18(4), 833-846. doi: 10.1007/s12119-014-9225-6
Lehmiller, J. J., VanderDrift, L. E., & Kelly, J. R. (2014). Sexual communication, satisfaction,
and condom use behavior in friends with benefits and romantic partners. Journal of Sex
Research, 51, 74-85. doi: 10.1080/00224499.2012.719167
Li, Y., & Samp, J. A. (2019). Sexual relationship power, safe sexual communication, and condom
use: A comparison of heterosexual young men and women. Western Journal of
Communication, 8391), 58-74. doi: 10.1080/10570314.2017.1398835
Lovejoy, M. C. (2015). Hooking up as an individualistic practice: A double-edged sword for
college women. Sexuality & Culture, 19, 464-492. doi: 10.1007/s12119-015-9270-9

HETERONORMATIVITY AND SEXUAL HEALTH 94
Madley-Dowd, P., Hughes, R., Tilling, K., & Heron, J. (2019). The proportion of missing data
should not be used to guide decisions on multiple imputation. Journal of Clinical
Epidemiology, 110, 63-73. https://doi.org/10.1016/j.jclinepi.2019.02.016
Martino, S. C., Collins, R. L., Kanouse, D. E., Elliott, M., & Berry, S. H. (2005). Social
cognitive processes mediating the relationship between exposure to television’s sexual
content and adolescents’ sexual behavior. Journal of Personality and Social Psychology,
89, 914–924.
McGinnis, J., & Harel, O. (2016). Multiple imputation in three or more stages. Journal of
Statistic Planning and Inference, 176, 33-51. doi: 10.1016/j.jspi.2016.04.001
Naruchitparames J, Gunes MH, Louis SJ (2011) Friend recommendations in social networks
using genetic algorithms and network topology. IEEE congress on evolutionary
computation (CEC), pp 2207–2214.
ODPHP. (2019). Determinants of Health. Retrieved on April 11, 2019 from
https://www.healthypeople.gov/2020/about/foundation-health-measures/Determinants-of-
Health#individual%20behavior
Planned Parenthood. (2019). What are the benefits of condoms? Retrieved on May 12, 2019
from https://www.plannedparenthood.org/learn/birth-control/condom/what-are-
thebenefits-of-condoms
Quinn-Nilas, C., Milhausen, R. R., Breuer, R., Bailey, J., Pavlou, M., DiClemente, R. J., &
Wingood, G. M. (2016). Validation of the sexual communication self-efficacy scale.
Health Education and Behavior, 43(2), 165-171. doi: 10.1177/1090198115598986
Radloff, L. S. (1977). The CES-D scale: A self-report depression scale for research in the general
population. Applied Psychological Measurement, 1, 385-401. doi: 10.13072/midss.120

HETERONORMATIVITY AND SEXUAL HEALTH 95
Rinaldi-Miles, A., Quick, B. L., & LaVoie, N. R. (2014). An examination of the principles of
influence on condom use decision making during casual sex encounters. Health
Communication, 19, 531-541. doi: 10.1080/10410236.2013.765295
Rosen, R. C., Catania, J., Pollack, L., Althof, S., O’Leary, M., & Seftel, A. D. (2004). Male
sexual health questionnaire (MSHQ): Scale development and psychometric validation.
Adult Urology, 64, 777- 782. doi: 10.1016/j.urology.2004.04.056
Rosen, R., Brown, C., Heiman, J., Leiblum, S., Meston, C., Shabsign, R., ... D’Agostino, R.
(2000). The female sexual function index (FSFI): a multidimensional self-report
instrument for the assessment of female sexual function. Journal of Sexuality and Marital
Therapy, 26(2), 191-208. doi: 10.1080/009262300278597
Schalet, A. T. (2011). Beyond abstinence and risk: A new paradigm for adolescent sexual health.
Women’s Health Issues, (S5-S7), 21-35. https://doi.org/10.1177/0265407519842337
Schroder, K. E., Carey, M. P., & Vanable, P. A. (2003). Methodological challenges in research on
sexual risk behaviors: II. Accuracy of self-reports. Annals of Behavioral Medicine,
26(2), 104-123. https://doi.org/10.1207/S15324796ABM2602_03
Schumacker, R. E., & Lomax, R. G. (2010). A beginner’s guide to structural equation modeling
(4th ed). New York, United States: Routledge, Taylor, & Francis Group.
Urban, J. B., & van Eeden-Moorefield, B. M. (2018). Designing and proposing your research
project. Washington, DC: American Psychological Association.
Urban, J. B., & van Eeden-Moorefield, B. M. (2018). Designing and proposing your research
project. Washington, DC: American Psychological Association.
van Eeden-Moorefield, B. (2018). Introduction to the special issue: Intersectional variations in
the experiences of queer families. Family Relations, 67, 7-11. doi: 10.1111/fare.1230

HETERONORMATIVITY AND SEXUAL HEALTH 96
WHO. (2019). Sexual health. Retrieved on May 12, 2019 from
https://www.who.int/topics/sexual_health/en/
WHO. (2019). The determinants of health. Retrieved on April 11, 2019 from
https://www.who.int/hia/evidence/doh/en/
Widman, L., Choukas-Bradley, S., Helms, S. W., Golin, C. E., Prinstein, M. J. (2014). Sexual
communication between early adolescents and their dating partners, parents, and best
friends. Journal of Sex Research, 51(7), 721-741. doi: 10.1080/00224499.2013.843148
Widman, L., Choukas-Bradley, S., Noar, S. M., Nesi, J., Garrett, K. (2016). Parent-adolescent
sexual communication and adolescent safer sex behavior: A meta-analysis. JAMA
Pediatrics, 170, 52-61. doi: 10.1001/jamapediatrics.2015.2731
Widman, L., Noar, S. M., Choukas-Bradley, S., Francis, D. B. (2014). Adolescent sexual health
communication and condom use: A meta-analysis. Health Psychology, 33(10), 1113-
1124. doi: 10.1037/hea0000112
Zielinski, R. (2013). Assessment of women’s sexual health using a holistic, patient centered
approach. Journal of Midwifery and Women’s Health, 58(3), 321-327. doi:
10.1111/jmwh.12044
Table 4.1
Participant Demographic Characteristics
Variable
Percent
Race
White
88.80%
Hispanic/Latina
6.40%
East Asian/ Asian American
2.10%
Native American/ Alaska Native
1.60%

HETERONORMATIVITY AND SEXUAL HEALTH 97
Black/ African American
1.10%
South Asian/ Indian American
1.10%
Middle Eastern/ Arab American
<1.00%
Education
High School/GED
4.30%
Some College
7.40%
Associate’s Degree
3.70%
Bachelor’s Degree
41.50%
Master’s Degree
28.70%
PhD, MD, DO, or advanced graduate work
12.80%
Other
1.60%
Income
< $25,000
5.90%
$25,000-$49,999
13.40%
$50,000-$74,999
19.80%
$75,000-$99,999
20.90%
$100,000-124,999
15.50%
> $125,000
24.60%
Attraction
Mostly Males
30.30%
Only Males
69.70
Health
Insurance
Yes
97.90%
No
2.10%
Table 4.2
Measurement Descriptive Statistics
Measure
Min
Max
M(SD)
α
SCSE
15
60
46.77 (8.80)
.91
SSB
8
32
19.13 (4.88)
.68
Het*
34
112
86.02 (17.30)
.91

HETERONORMATIVITY AND SEXUAL HEALTH 98
Anx*
3
21
17.40 (4.06)
.69
Dep*
14
40
31.93 (5.66)
.86
PSH
1
4
3.72 (.56)
---
Safe
2
5
4.80 (.56)
---
SFW*
9
45
24.04 (5.83)
.81
SexSat
6
30
21.05 (6.78)
.94
STI*
3
6
5.89 (.53)
.79
Note. *Scales were recoded so that higher scores indicate better sexual health.
SCSE= sexual communication self-efficacy, SSB= safe sex behaviors, Het=
heteronormativity, Anx= Anxiety, Dep= Depression, PSH= perceived physical sexual health,
safe= safety, SFW= sexual functioning, SexSat= sexual satisfaction, STI= Sexually transmitted
infections
Table 4.3
Correlations of Variables
Measure
SCSE
SSB
Het
Anx
Dep
PSH
Safe
SFW
SexSat
STI
SCSE
_--
SSB
.13
--
Het ^
-.03
-.07
--
Anx ^
.32**
-.26**
-.02
--
Dep ^
.11
-.12
-.11
.27**
--
PSH
.28**
-.23**
.06
.30*
.20**
--
Safe
.13
-.14
-.09
.16*
.32**
.21**
--
SFW ^
.29**
-.03
-.16**
.24**
.16*
.29**
-.09
--
SexSat
.34**
-.18*
-.02
.22**
.31**
.18*
.42**
.40**
--
STI ^
.11
.04
-.04
.06
.10
.10
-.06
.056
.09
--
Note. ^ Scales were recoded so that higher scores indicate better sexual health.
*p<.05 **p<.001
SCSE= sexual communication self-efficacy, SSB= safe sex behaviors, Het= heteronormativity, Anx=
Anxiety, Dep= Depression, PSH= perceived physical sexual health, safe= safety, SFW= sexual
functioning, SexSat= sexual satisfaction, STI= Sexually transmitted infections

HETERONORMATIVITY AND SEXUAL HEALTH 99
Table 4.4
Unstandardized estimates, standardized estimates, and standard errors of the base mediation
model, low heteronormativity model, and high heteronormativity model.
Paths
Base Model Un.
Stand. S.E.
Low Heteronormativity
Un. Stand. S.E.
High Heteronormativity
Un. Stand. S.E.
SSB CSE
.08 .14 .04
.01 .03 .06
.15 .26 .06
Compsex SSB
-.29* -.43* .06
-.28* -.36* .08
-.41* -.67* .12
Compsex CSE
.23* .74* .05
.32* .79* .06
.20* .56* .06
Note. * indicates p<.05
Un.=Unstandardized, Stand= Standardized
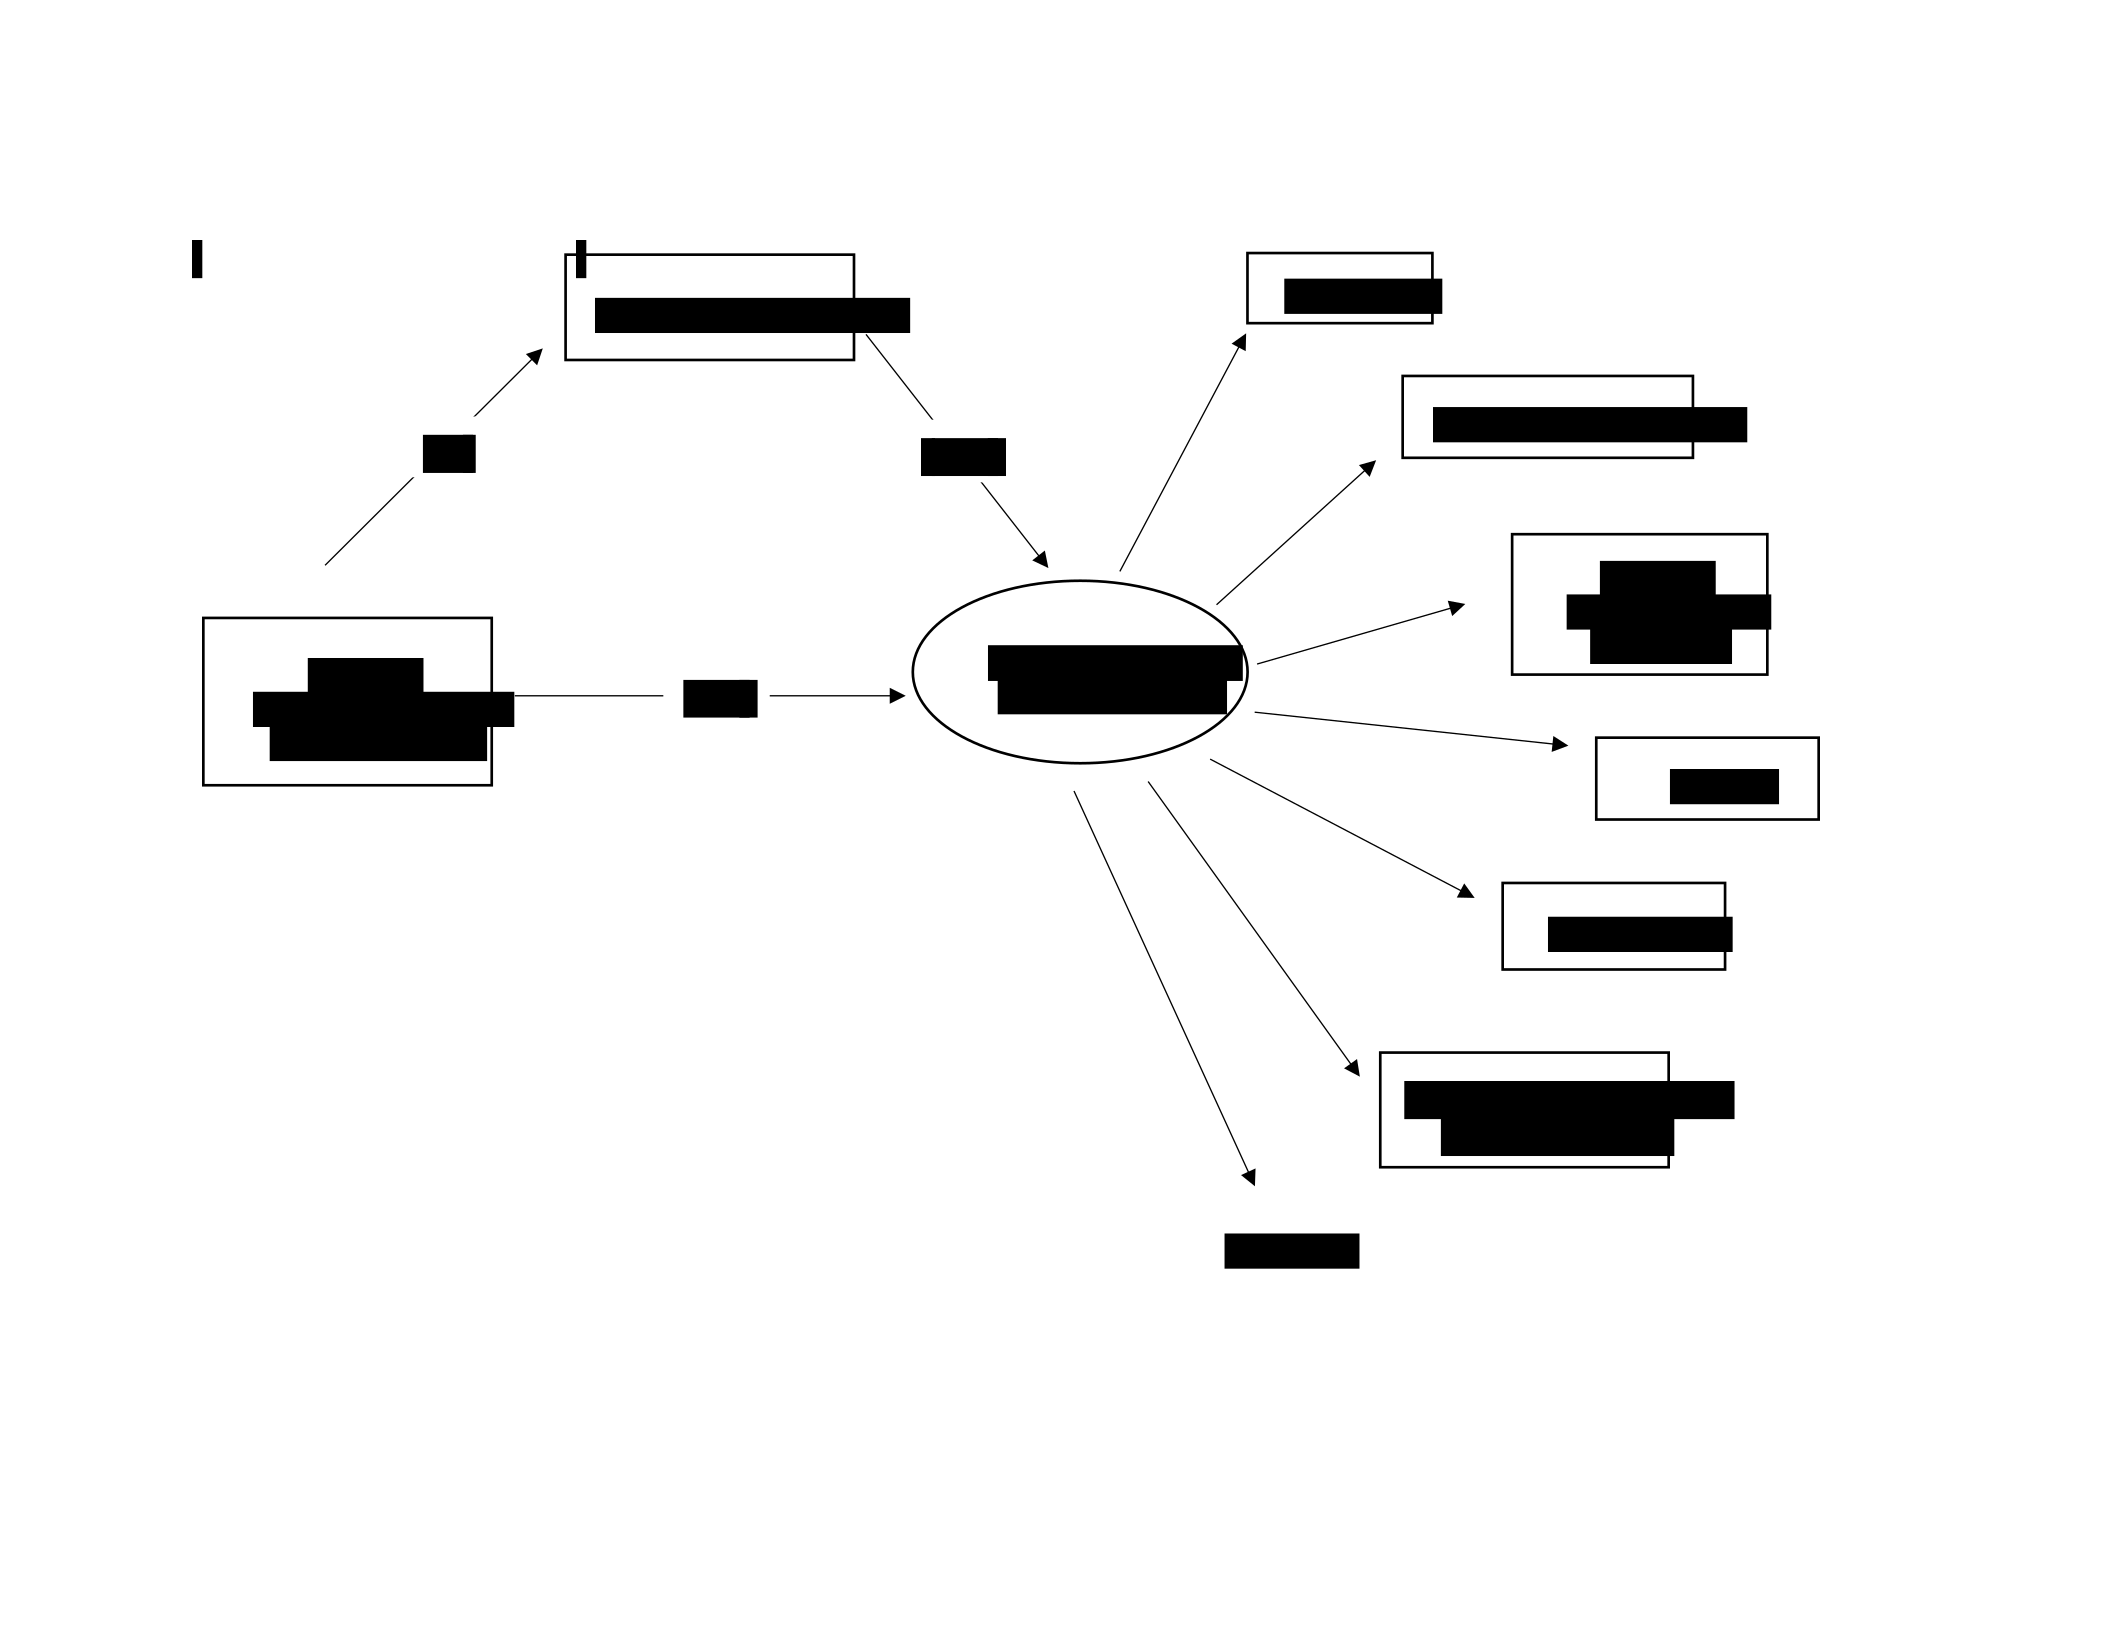
HETERONORMATIVITY AND SEXUAL HEALTH 100
Figure 4.1. Base mediation model with parameter estimates
* Indicates p < .05
Sexual
Communication
Self-Efficacy
Safe Sex Behaviors
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived physical
sexual health
Anxiety
.14
-
.43*
.74*
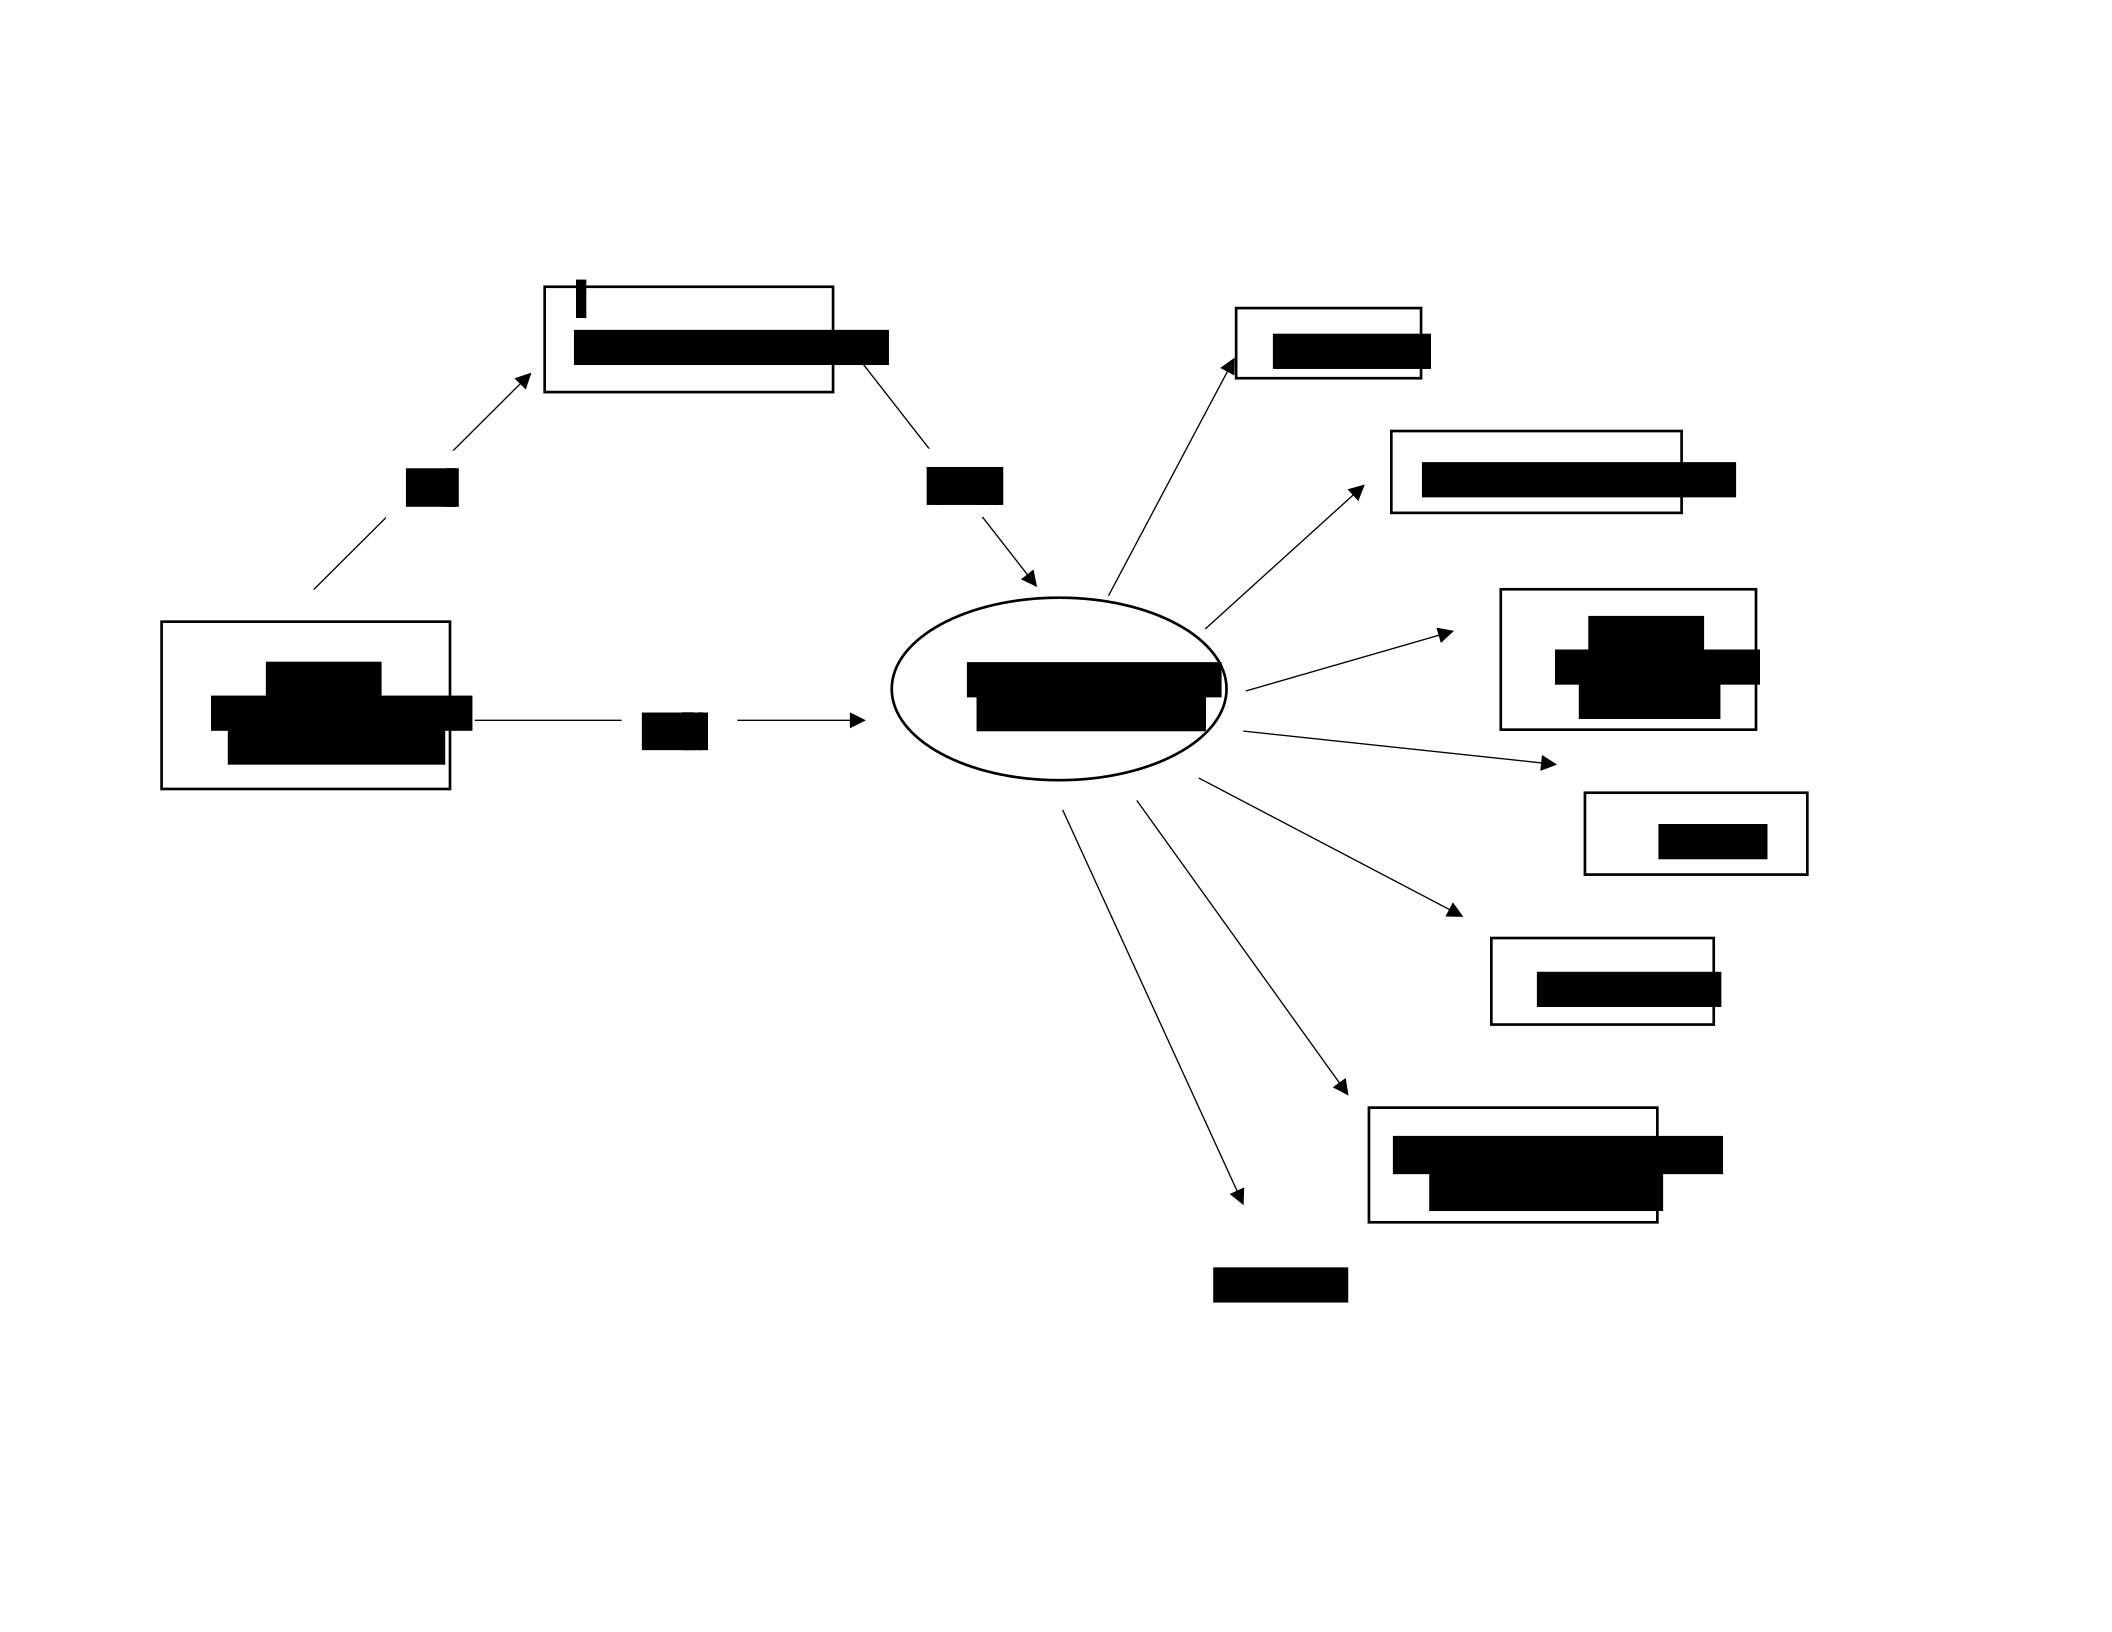
HETERONORMATIVITY AND SEXUAL HEALTH 101
Figure 4.2. Low internalized heteronormativity model with parameter estimates *
indicates p < .05
Sexual
Communication
Self-Efficacy
Safe Sex Behaviors
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived physical
sexual health
Anxiety
.03
-
.36
*
.79
*
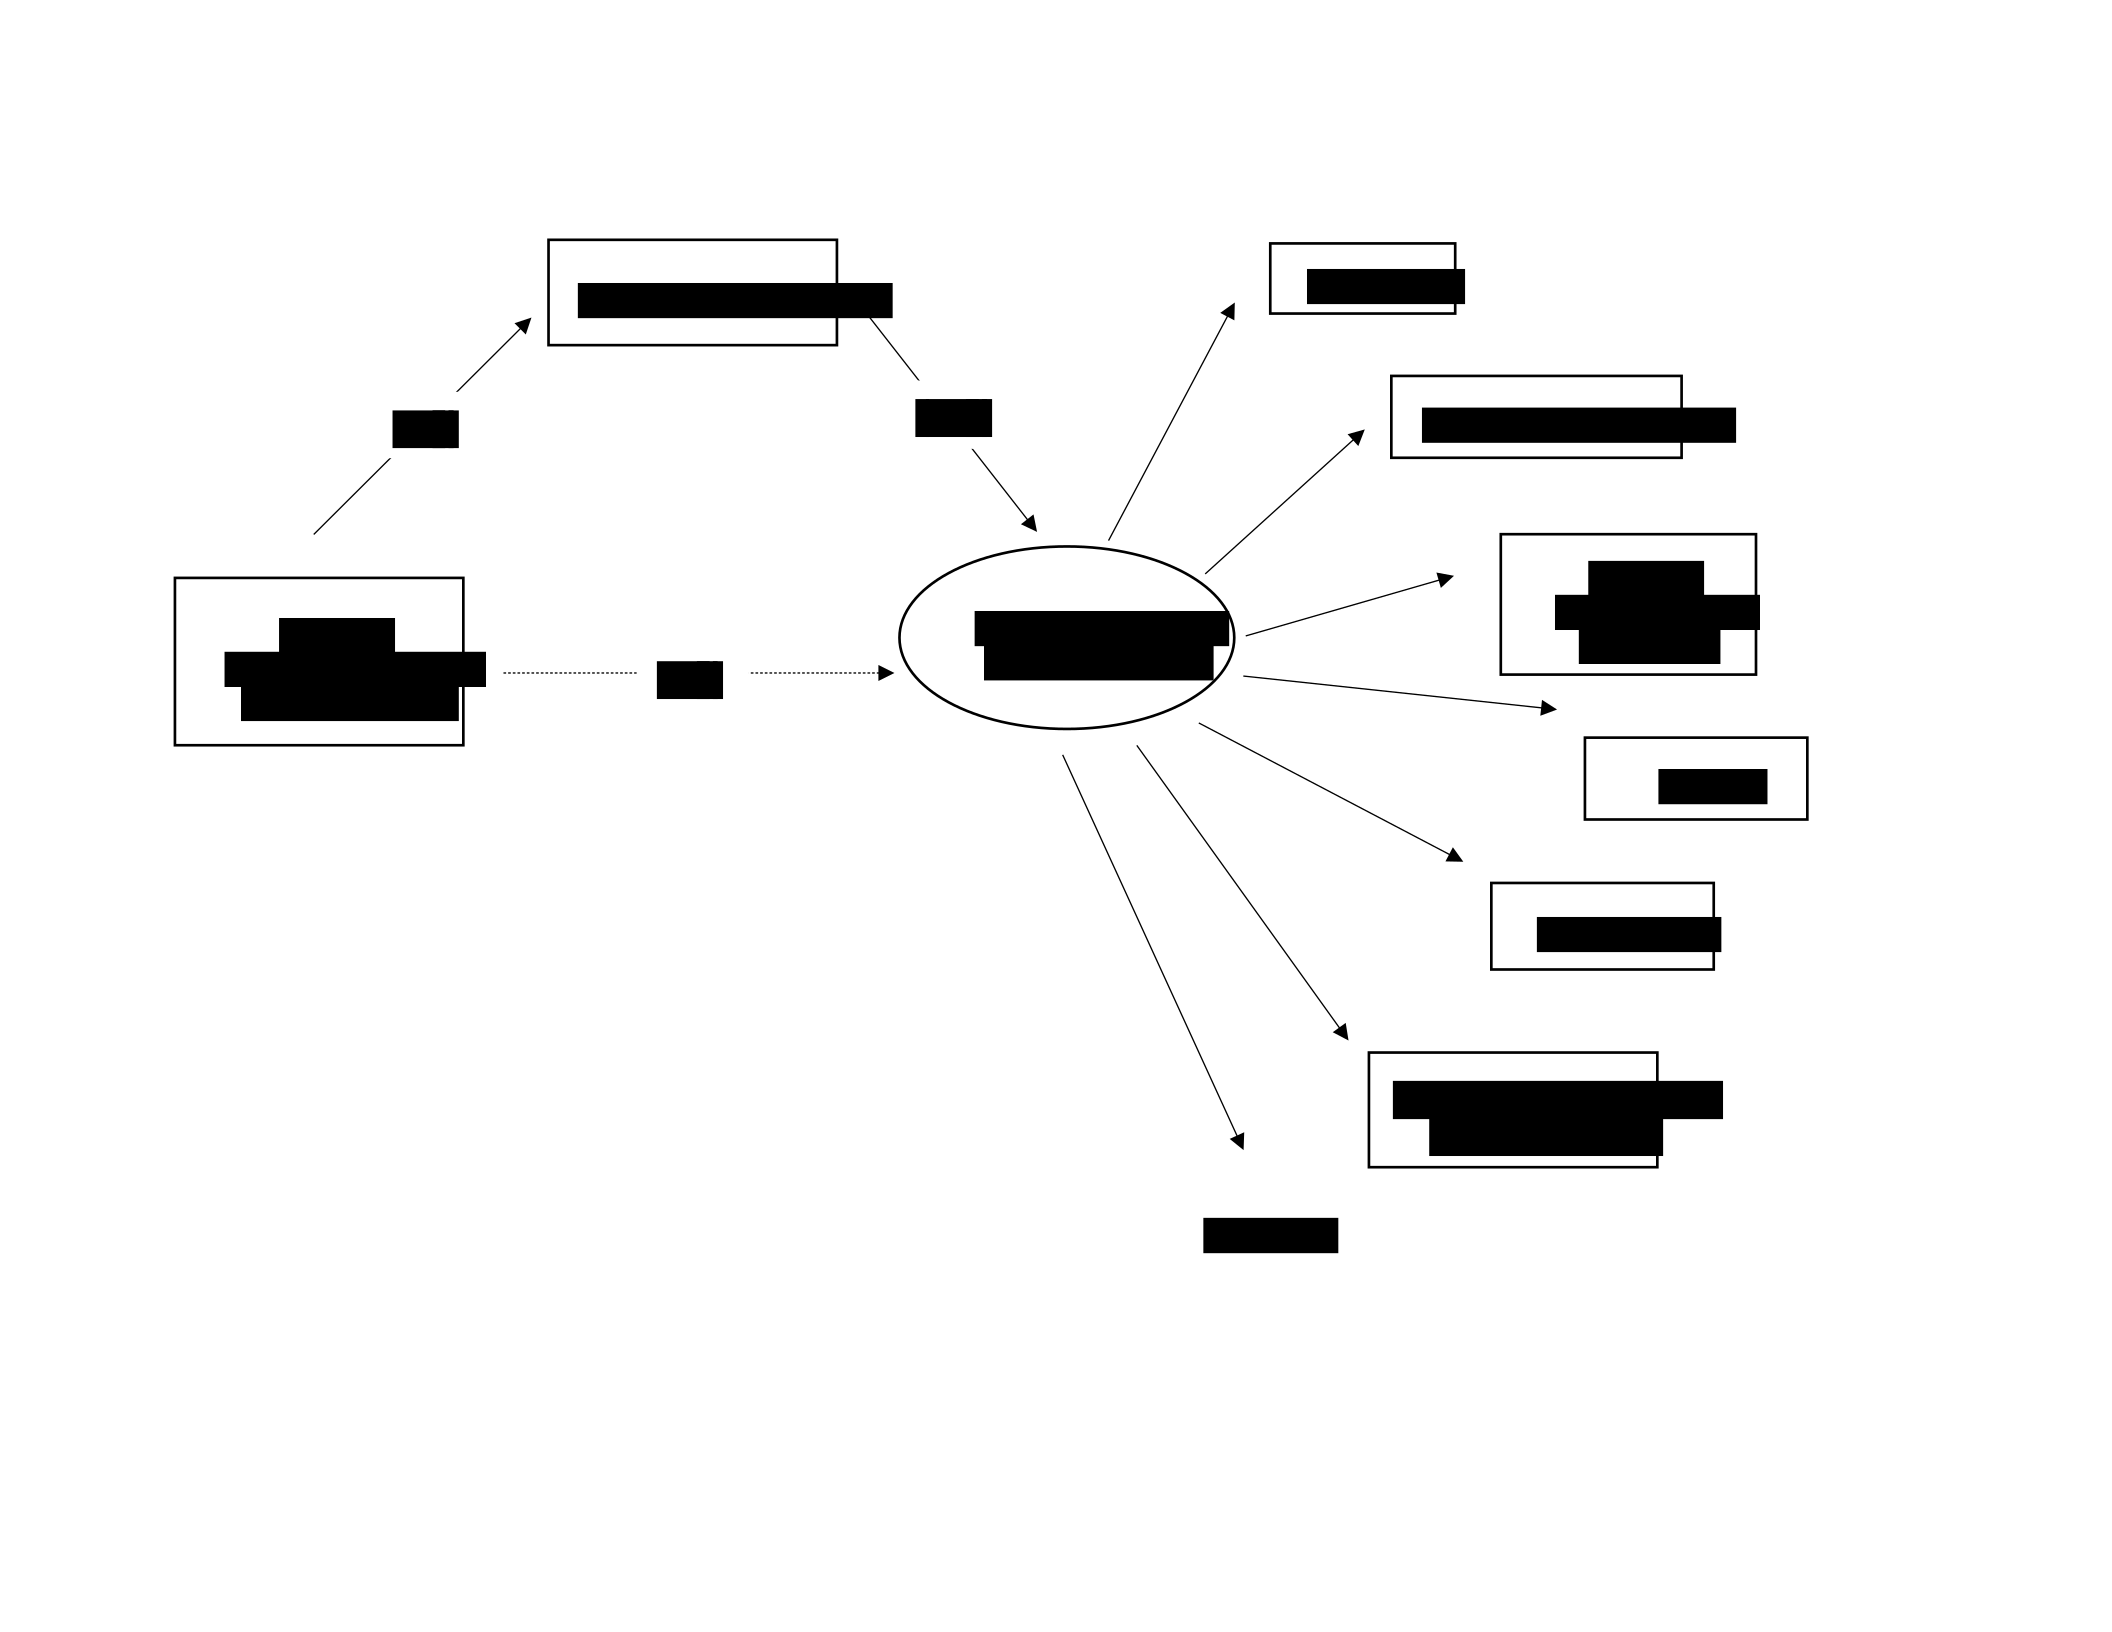
HETERONORMATIVITY AND SEXUAL HEALTH 102
Figure 4.3. High internalized heteronormativity model with parameter estimates
* indicates p < .05
Sexual
Communication
Self-Efficacy
Safe Sex Behaviors
Comprehensive
Sexual Health
STI/ HIV
Sexual Functioning
Sexual
Satisfaction/
Pleasure
Safety
Depression
Perceived physical
sexual health
Anxiety
.26
*
-
.67
*
.56
*

HETERONORMATIVITY AND SEXUAL HEALTH 103
CHAPTER 5: DISCUSSION
Human sexuality is shaped and understood through a series of individual behaviors,
interpersonal exchanges, and social constructions-- biology, mental health, and social exchanges
all contribute to human sexuality and sexual experiences (WHO, 2010). In other words, human
sexuality is more than simply sexual behavior-- it encompasses an entire person interacting with
others in context. Therefore, it makes sense that in order to best understand sexual health we
must conceptualize (and measure) it comprehensively. This is consistent with the WHO’s (2019)
assertion that we should consider the individual, interpersonal, and social factors that
collectively influence health and can lead to health disparities. To date, the extant literature
rarely addresses these calls in any single study. Additionally, much of the extant literature
minimizes sexual health to the absence of disease (CDC, 2020) and unintended pregnancy
(Guttmacher, 2019). From these narrow conceptualizations of sexual health, research identified a
number of health disparities that exist across these two biological domains for women (i.e.,. STI
diagnoses, and unintended pregnancy). Importantly, although research has identified these
disparities, few understand why these disparities exist outside of behavioral mechanisms.
Thus, the first aim of this study was to create and validate a measure of comprehensive
sexual health grounded in the World Health Organization’s (WHO; 2019) definition of sexual
health. By using a comprehensive measure, rather than a single biological indicator of health
(i.e., STI diagnoses), research can begin to parse apart different interpersonal and social factors
that contribute to and perpetuate sexual health disparities. Therefore, the second aim of this
study used this comprehensive measure of sexual health to model how cultural heteronormativity
(which often shames women for their sexuality; Easton & Hardy, 2009) influences

HETERONORMATIVITY AND SEXUAL HEALTH 104
comprehensive sexual health outcomes across diverse women (i.e., queer and heterosexual
women). Results from these models suggest that sexual communication self-efficacy strongly
predicts comprehensive sexual health outcomes for women, regardless of their sexual
orientation. However, to some extent, heteronormativity impacts these processes potentially
contributing to sexual health disparities among women.
Comprehensive Measurement of Sexual Health
The first significant contribution of this study was creating and validating a parsimonious
measure of comprehensive sexual health grounded in the WHO’s (2019) conceptual definition.
By creating a comprehensive measure of sexual health, future research may begin to ask
questions about individual, interpersonal, and social influence on comprehensive sexual health,
which considers sexuality as more than biology. Specifically, future research can ask questions
about the person while considering the context within which they live. By asking question in this
way, research may find, processes that contribute to non-biological indicators of sexual health
disparities, specific to women, such as orgasm gaps (e.g., Frederick, John, Garcia, & Lloyd,
2017) feelings of safety in consensual sexual encounters (Jozkowski & Wiersma, 2015), and
sexuality specific anxiety and depression (Kalmbach, Kingsberg, & Cielsa, 2014). Along those
lines, research may begin to holistically understand the role that culture plays in comprehensive
sexual health outcomes across diverse groups. This dissertation explored this idea in study two
and study three.
Focusing on Communication Rather than Safe Sex Behaviors
Along those lines, this program of research used the aforementioned comprehensive
measure of sexual health in two models to understand how communication self-efficacy and safe

HETERONORMATIVITY AND SEXUAL HEALTH 105
sex behaviors contribute to comprehensive sexual health outcomes. Results suggested that when
we consider the sexual health of the entire person (i.e., biological, mental, and social sexual
health) safe sex behaviors are not necessarily as predictive of sexual health outcomes as the
extant literature suggests (e.g., Li & Samp, 2019). In fact, communication self-efficacy, which is
an individual’s belief about their ability to communicate about sexuality, was the strongest
predictor of comprehensive sexual health outcomes for both heterosexual and queer women. By
using a comprehensive measure of sexual health, we learned that safe sex behaviors may only
contribute to biological indicators of sexual health, but not necessarily other domains of sexual
health. Specifically, being able to communicate may not directly prevent STIs, because STIs are
a biological indicator of sexual health (CDC, 2020). But it may be able to reduce anxiety and
depression related to sexuality (e.g., Brassard, Dupuy, Bergeron, & Shaver, 2015; Dobkin,
Leiblum, Rosen, Menza & Marin, 2006), increase sexual satisfaction (e.g.,Woloski-Wruble,
Oliel, Leefsma, & Hochner-Celnikier, 2010), and increase feelings of safety in a sexual
encounter (Jozkowski & Wiersma, 2015). Therefore, when the conceptualization of sexual health
is comprehensive, communication self-efficacy may be more predictive of comprehensive sexual
health than engaging in the traditional safe sex behaviors.
Cultural Influence of Heteronormativity
Finally, these models presented ways through which culture influences comprehensive
sexual health outcomes. For both queer and heterosexual women, sexual health processes (i.e.,
communication self-efficacy and safe sex behaviors) worked differently for women with high
internalized heteronormativity compared to those with low internalized heteronormativity. In
other words, heteronormativity influenced individual and interpersonal sexual health processes

HETERONORMATIVITY AND SEXUAL HEALTH 106
for queer and heterosexual women. Thus, there is an interaction between cultural messages and
gender (Easton & Hardy, 2009). Specific to heteronormativity, this demonstrates how
constrictive and stigmatizing messages about women and their sexuality can actually alter
processes that would lead to better comprehensive sexual health outcomes. It’s important to note
that heteronormativity is a mechanism through which patriarchy and control is upheld
(D’Emilio, & Freedman, 2012; Easton & Hardy, 2009) which may put women’s health at risk,
particularly if they do not have high sexual communication self-efficacy. Patriarchal structures
have historically (and currently) attempted to control women’s sexuality and their sexual health
through stigmatizing processes such as slut-shaming (D’Emilio, & Freedman, 2012). This study
shows how that can be a serious hinderance to women’s comprehensive sexual health outcomes.
Empowering women to communicate, advocate for their bodies, and control their health, may be
ways in which women can fight back against heteronormative structures (Easton & Hardy,
2009). In other words, there is a clear emergent link that culture plays a role in health disparities.
Thus, future research must consider cultural context and the messages women receive about
their sexuality, to find ways through which to improve comprehensive sexual health for women.
For women with high internalized heteronormativity, it may critical to improve sexual
communication self-efficacy; without it, it is possible that they may not be able to communicate
about other domains of sexuality, ultimately hindering their comprehensive sexual health
outcomes (Quinn-Nilas et al., 2016).

