


TRACKING THE HUMAN:
POSTHUMANISM,
ETHICS, AND CRITIQUE
IN HEALTH TRACKING
TECHNOLOGIES

INTRODUCTION
The Star Trek episode “Space Seed,” which first aired in 1967, opens with the
USS Enterprise crew beaming onto a mysterious ship filled with sleeping people, all
within glass containers. Dr. McCoy pulls out a black box and points it toward one of
the sleeping bodies. The box allows him to collect vital signs such as temperature and
heart rate, even though the physical body of the person is isolated away from the
machine. These vital signs initially read as typical, but the heart rate quickly drops,
allowing McCoy to identify a potential medical emergency and act quickly to free the
body from its cryogenic chamber. The person trapped is saved from death. Ironically,
he turns out to be the future nemesis of the crew, the genetically modified Khan.
Although the device that McCoy uses to diagnose and save Khan, called a
medical tricorder, is almost unremarkable amongst the other retro-futurist technology
of Star Trek, it is perhaps one of the most significant. It allows for a portable solution
to quickly and accurately read medical metrics while also continually processing these
metrics for real-time feedback on the patient’s health. The usefulness of the medical
tricorder may be hidden behind much of the other flashier Star Trek technology like
phasers or transporters, but it has not been lost on the contemporary medical
community. Practitioners currently rely on a number of different, bulky devices to
perform the same tasks as the tricorder, including thermometers, heart rate monitors,
and blood pressure cuffs. Creating a portable all-in-one device would greatly aid in the
ability of practitioners to assess and diagnose patients easier, more frequently, and in -
1

2
less accessible locations. In the past few years, industry efforts have been mobilized to
create such a device.
The XPrize Foundation is one such effort. The foundation has created a $10
million award for the first company which successfully creates a product that
approximates much of the functionality behind the Star Trek device. Appropriately
called the Qualcomm Tricorder XPrize, the reward requires that the device must be
small and portable, while still able to (1) accurately diagnose 16 health conditions
(anemia, atrial fibrillation, chronic obstructive pulmonary disease, diabetes, Hepatitis
A, leukocytosis, pneumonia, otitis media, sleep apnea, stroke, tuberculosis, urinary
tract infection, absence of conditions, airborne allergens, cholesterol screen, food-
borne illness, HIV screen, hypertension, hypothyroidism/hyperthyroidism, melanoma,
mononucleosis, osteoporosis, Pertussis, shingles, and strep throat) and (2) monitor five
vital signs (blood pressure, heart rate, oxygen saturation, respiratory rate,
temperature).1 Though this is a tall order, there are currently seven finalists working
toward a solution. Scanadu is the forerunner among these finalists, launching a
successful Indiegogo campaign in 2014 and shipping to early backers in 2015. The
device is called the “Scout” and, after being placed on the user’s forehead for a few
seconds, provides information on heart rate, core body temperature, blood
oxygenation, and systolic and diastolic blood pressure.2 The data is then sent to a
mobile app, where the user can access the raw data as well as commentary by the app
that helps interpret the data.

3
Much like the medical tricorder in Star Trek, Scanadu hopes that their Scout
product will make gathering medical data on individuals easier by putting it in the
hands of the patients themselves. The website boasts that the device will be “your
doctor’s new best friend” and that the user can “check [their] health as easily as [their]
email.”3 The concept behind the device seems to be to bring the hospital into the daily
life of the individual and to promote a healthy style of living.
On first glance, Scanadu’s focus on self-monitoring appears to be in line with
Michel Foucault’s claim that clinical medicine is concerned with not just curing
illness, but in placing an individual under surveillance to understand their issues. This
constant observation is termed the “medical gaze” and sees illness through direct
observation of bodies, rather than through laboratory controlled experiments that
isolate viruses, bacteria, cells, or other factors that make up the disease in order to
understand it. A technology like Scanadu would exemplify Foucault’s notion of the
gaze, extending the ability of medicine to observe the individual beyond the walls of
the hospital itself and away from a physically-present practitioner that conducts tests.
A medical tricorder-type device would allow the individual to continue medical
surveillance within their own home, incorporating the gaze within everyday life and
allowing the individual to order their lives in a way that reflects medical
recommendations.
The danger of the medical gaze lies in the institutionalization of medical
knowledge, which becomes concerned with “completed scanned multiplicity of
individual facts” rather than “completely observed individuality.”4 With a large

4
amount of observed data, medicine becomes concerned with creating the idea of a
normalized, healthy human and then attempts to order the life of individuals to fit that
particular conception through guidelines for healthy living. Scanadu and the image of
a medical tricorder would seem to fit well with Foucault’s normalizing medical gaze:
it would provide medical researchers with large amounts of data from many
individuals that could be processed to either find the typical human or could be fed
back to the individual to show how they are falling short of ordering their lives in the
“proper” manner.
However, the discourse surrounding Scanadu and other health-monitoring
technologies disrupts these notions significantly. Unlike the medical tricorder in Star
Trek and many contemporary health-monitoring devices, Scanadu is meant to be used
by the individual to collect data for both the practitioner and the individual to analyze,
ostensibly allowing the individual to be more than the target of a medical gaze. The
Scanadu website asks the visitor to “Imagine a future where you can know yourself
best” and proclaims that “Finally, information about our body is not locked away
inside the walls of a hospital.”5 Moreover, the Scout is “designed to provide you with
access to valuable data which your body provides every day” and will allow “anyone
to capture important physiological data.” Here, the focus is not on collecting data for
the hospital, but collecting data that the user can analyze, providing the opportunity
for a “completely observed individuality” rather than a “completely scanned
multiplicity of individual facts.”

5
While Scanadu remains under development, a large market for wearable
devices with similar, but more limited capabilities has emerged in recent years. Yearly
revenue for wearables is projected to reach 19 billion dollars in 2018, a tenfold
increase since 2013.6 Devices that specifically track health metrics make up a
significant portion of this market, as accelerometers like Fitbits become commonplace
and as health-tracking software gets automatically bundled with the latest iOS release.
Scanadu and market-ready tracking devices allow the individual to carry a greater
responsibility for their own healthcare, but also potentially gains a greater freedom to
manage their own care in ways outside of strict medical control. Much like Scanadu
seeks to reorganize the relationship between medical practitioner and patient, wearable
health tracking devices provide an opportunity to examine how medicine’s idea of a
“normal” human body can be called into question as individuals begin to monitor their
own health.
Even as health tracking technologies provide an opportunity to open up the
medical definition of the human, they also encourage their users to engage in two
potentially harmful processes that replicate a single, medically-sanctioned idea of the
human. The first comes from placing responsibility on the individual to manage their
own health through increased modes of surveillance and oversight. Through these
methods, individuals are pushed toward replicating the social idea of what can be
identified as a “normal” individual or, to borrow Rosemarie Garland Thomson’s term
from disability studies, the “normate.”7 Examples of this include patients with chronic
conditions who are recommended a set of self-care procedures to keep their condition

6
under control or health tracking devices like the Fitbit that set a standard number of
steps to walk in a day for the user to be “healthy.” In these cases, medical knowledge
sets a standard by which people are supposed to order their lives and care for
themselves. Such a standard replicates a generic idea of what a proper “human” can be
and places the onus on the individual to follow through with acting accordingly to
preserve their health.
The second process emerges when individuals are converted into quantifiable
metrics, which can include steps taken, calories consumed, genetic markers, happiness
levels, or anything else that can be measured. An individual could then be excluded
from societal, economic, or medical spheres based on how favorably their metrics
compare to a baseline. Examples of this include long-term loans being denied to
people exhibiting genetic markers with a high likelihood of developing early-onset
fatal diseases or healthcare being denied to individuals who do not record a certain
amount of exercise on a tracking device.
However, in practice, placing responsibility on the individual to manage their
health also results in a greater freedom to manage medical self-care regimes in ways
other than those prescribed. Case studies of diabetics, for example, show that doctor
recommendations often get misunderstood or ignored because they do not fit easily
into the busy lives of individuals. As a result, the individual makes assessments and
choices about how to assemble a self-care regime. Health tracking technologies get
used in a similar way, as groups like Quantified Self take the data from Fitbits, sleep
trackers, and other wearables to create their own, unique protocols for losing weight,

7
sleeping, or any number of other tasks. The difference between the ideal of self care
techniques and the ways that those techniques play out in every day life point to a
disjunct where medical technologies encourage greater oversight and surveillance, but
in a way that puts the responsibility of analysis in the hands of the individual,
allowing them to come to conclusions through analyzing a large dataset that applies
only to their situation. In turn, the idea of a normate human also breaks apart, opening
itself up to a multitude of different configurations.
With the ability to apply large-scale data observation and analysis on the
individual level, it is now possible to create the image of a “normal” human that
applies only to a single individual. In turn, institutions such as medicine and
government that operate based on the assumption that there is a normate model of the
human must reconfigure their engagement with individuals. It is the twofold purpose
of this dissertation to examine how contemporary medical self-tracking technologies
begin to change the idea of the human and how institutions deal with this newly
reconfigured individual who does not necessarily embody the normate idea of the
human.
Chapter One will trace the emergence of contemporary ideas of the human and
how both medicine and technology have reconceptualized the human. This discussion
will provide a basis for shaping later analysis on how medical self-tracking
technologies are used, as well as the larger theoretical implications with society and
institutions. Taking Foucault’s cue that contemporary medicine’s idea of the human
has roots in eighteenth century thought, this chapter will focus on the human’s

8
appearance in Cartesian and Enlightenment philosophy and later articulation in the
development of technology and medicine. Descartes initial starting point, as a division
of mind and body, has been influential in the way that medical discourse has
continued up until the twenty first century. For Descartes, the human was the only
entity capable of rational thought and stood as a unified entity apart from the world
around it.8 Other objects such as animals or machines may occasionally appear to
possess reason, but this is just an illusion created by instinct and pre-set mechanisms,
respectively.9 Kant took this idea further, claiming that humans are responsible for the
value, form, and meaning of the world as a whole.10 Both thinkers created a radical
type of anthropocentrism that resulted in the formulation of a “proper” type of human
that possesses rationality and stood as a unified being at the center of the world. Such
a theorization had extreme consequences when individuals did not fit that definition
of human. Michel Foucault points to this in his writings on madmen, who allegedly
did not possess reason and the techniques of power utilized by institutions to
encourage such individuals to act in ways that made them proper, healthy humans.11
Thinkers like Michel Foucault, Katharine Hayles, Neil Badmington, and David
Roden have recognized the potentially dangerous applications of humanism and
attempted to move away from humanism in recent years. While Foucault has focused
primarily on how the human has been (re)configured through various institutions,
Hayles, Badmington, Roden, and have looked at how contemporary technology has
changed conceptions of the human – specifically with regards to feminist,
postcolonial, and racial issues – engaging in what they call “posthumanist” critique.

9
Though the posthumanists are often influenced by Foucault, they typically deal with
technologies such as artificial intelligence, games, and social networks rather than
specifically medical technologies. Putting them in dialogue with Foucault’s
identification of medicine as a significant point at which humanism emerges has the
potential to show how contemporary medical technologies change ideas of the human.
The chapter, therefore, examines the different ways that posthumanism and the
related theories of transhumanism and Object Oriented Ontology have attempted to
get beyond the radical anthropocentrism of Descartes and Kant through a focus on the
individual’s situatedness within an environment of non-human actors. But, as
Halliwell and Mousey and Badmington point out, posthuman theories are not entirely
“post” because they do not completely jettison the idea of the human. Instead of trying
to remove the idea of the human entirely, chapter one looks to Foucault’s articulation
of the divide between the Enlightenment as an ethos of self-critique and the humanist
doctrine of a normalized, ideal figure of Man. This difference, typically collapsed in
posthumanist critiques of humanism, will be the basis of a move to ask if it is possible
to view the human as a type of subject involved in constant self-examination within a
larger context that constantly disrupts notions of an over-arching normalization.
Moreover, the chapter asks if it is possible to have a sense of ethics and justice –
qualities intimately tied with humanism – without the central, unified figure of Man.
The second chapter will take Foucault’s lead in looking to medicine to find a
type of subject involved in a form of self-critique that calls into question the
anthropocentric humanist formulation of the human. While this dissertation would not

10
disagree with the possibility of self-critique happening in short-term medical
interventions like treating a wound or seasonal flu, examining how self-critique plays
out over individuals living with disease brings forward more of the issues of how
patients deal with illness and self-care. These individuals are forced to (1) adhere to a
larger medical idea of what the model patient and “healthy” individual should be,
much in the way that humanism presents a model human and (2) take on much of that
responsibility themselves of producing and maintaining health, as in the ideal Kantian
individual who makes their own decisions. Examining case studies of how patients
with chronic diseases manage this tension provides a concrete instance of how
humanist and Enlightenment ideals are collapsed within contemporary medical
discourse, yet still opposed in many ways.
This chapter will take diabetic patients as the primary focus, as they must
constantly engage in self-care practices directed by medical standards, even if they are
also not completely restricted in their daily lives. Except in the most advanced and
extreme case of the disease, most diabetics are not bound to their homes or have
extremely visible signs of the disease. They are able to act as model humanist humans
in many ways, which also allows them assume a large degree of freedom in managing
their own disease, often pushing the boundaries of medical oversight.
By looking at case studies of diabetics, this chapter examines how self-care
affects a diabetic individual’s life over the long term and how medical practice has
increasingly moved to the home, requiring patients to constantly monitor their health.
As patients are required to do more of the day-to-day operations of dealing with their

11
disease, doctors engage in different methods to attempt to get the patients to care for
themselves in particular ways. One of these is concordance, where the doctors
promote an “open exchange of beliefs about medicine” in order to convince (rather
than order) the patient to perform particular methods of self-care when they are away
from the hospital.12
However, even with a less paternalistic model of care that has as its goal
actively involving patients in decision making processes, patients still do not precisely
follow the doctor’s orders. This chapter uses case studies found in medical papers to
look at the different ways that patients go about critiquing their own regimes of self-
care while also engaging with the medical community’s reaction to the various
regimes. By using case studies, it will be possible to show the divide between how
patients manage their condition through day-to-day operations, while also providing
the medically-sanctioned assessment of those self-care regimes.
Some of these regimes will be shown to be completely patient-directed and
against the orders of the doctor (such as patients believing that their diabetes needs to
be fed high amounts of sugar constantly). Others will modify the recommendations of
the doctor to fit their own needs and beliefs (for example, taking the prescribed
insulin, but modifying the dosage). The most important way of changing the way care
is administered will be shown to be through the examples of Vivienne Ming and Doug
Kanter, who both used contemporary health tracking technologies to monitor their
illness and collect large amounts of data. Though this data is similar to the type
collected by health institutions, it is analyzed primarily by the patients themselves and

12
allows them to create a new regime of care that is personalized and not always aligned
with medical recommendations. This change in how medical care is enacted creates a
situation whereby the rational, unified figure of the human breaks down, replaced by a
unique type of individual that constantly engages in self-critique, does not fit a
normalized model of “the human,” and is situated amongst a number of different,
often non-human actors.
The type of care Ming and Kanter engage in is further theorized in Chapter
Three by looking at self-reported case studies from the group known as Quantified
Self. The tagline of Quantified Self is “self knowledge through numbers,”13 a slogan
that equates the self with the data it produces by going about various activities
throughout the day. Quantified Selfers collect data about processes ranging from
steps taken to places visited to microbes in the gut to the amount of work done in a
particular time. These datasets can be visualized and compared to each other to gain
insight into an individual’s unique circumstance. Case studies provide specific
examples for how these datasets play out.
Where examining the self-care techniques of diabetics in Chapter Two looked
at a way that medical recommendations are modified and put into practice in different
ways, case studies of Quantified Selfers presented in Chapter Three demonstrate how
individuals create their own methods of self-care outside of specific medical
recommendations. These methods of self-care may have a loose basis in medical
studies or doctor recommendations, but many of them become highly personalized
and do not adhere to the universal, normate idea of how a patient should respond to

13
interventions into their way of living. By identifying ways that alternative self-care
practices emerge, this chapter begins to show how the concept of a “human” can be
retained, but also not generalized to a larger, universalized idea of “the human” that
must provide the blueprint for all individuals to order their lives.
Chapter three claims that while the data collecting within Quantified Self
seems to be a type of self-surveillance and a way of intensifying self-care practices
that make someone into a “normal” human, its effects are altogether different in
practice. Quantified Self proves to be an application of biopower, a technique of
power identified by Foucault as a way to track metrics related to the lives and bodies
of a population: births, deaths, overall health, and factors that cause these to vary.
These statistics provided a basis upon which institutions could create guidelines for
how individuals should order their lives. In the case of Quantified Self, however,
institutional authority is not just reproduced over the individual through tracking
health metrics. Instead, technologies normally applied to track populations are limited
only on the individual level. This results in an attempt to subvert the creation of an
over-arching, abstract concept of what a “normal” human would look like, which
could in turn be used as a mechanism to control populations.
This chapter takes as its starting point the three main characteristics of
biopower identified by Nicholas Rose and Paul Rabinow, two of the most prominent
contemporary commentators on biopower. Their conclusions are analyzed along with
corresponding Quantified Self projects to show that while QS generally fits into their
notion of how biopower operates, it operates on the individual level rather than on the

14
level of the population. Ben Finn’s attempt to track and learn about how different
variables affect his sleep demonstrates Rose and Rabinow’s claim that biopower
creates truth discourses about the vital character of human beings. However, in Finn’s
case, the truth discourse created about sleep patterns only applies to Finn’s unique
sleeping situation and can only be used as a starting point for other Quantified Selfers’
studies of their own sleep patterns. Likewise, Kim McCurdy’s analysis of her own
chronic condition comes out of a medical necessity to work on her individual habits in
order to avoid falling ill. It illustrates Rose and Rabinow’s claim that biopower works
by providing a strategy for intervention on large groups of people in the name of
health. However, McCurdy’s case presents a unique situation because she utilizes data
collection methods normally used to monitor populations on a single individual –
herself – creating an intervention in the name of health that applies to a population of
one. Lastly, Nancy Daugherty’s project presents a realization that Quantified Self
projects mostly serve to encourage an active participation in mindfully attending to
oneself through the act of tracking, rather than a specific roadmap to fix a particular
issue. This lines up with Rose and Rabinow’s point that biopower is the process by
which individuals engage in “modes of subjectification” where they work on
themselves according to certain practices of the self.14 In each case, the Quantified
Self project engages in a form of biopower, but analyzes the data of a single
individual to create a truth discourse that is limited to a single individual, rather than
generalized to fit the population as a whole.

15
Chapters Two and Three illustrate how individuals work alongside medical
technologies to create new forms of subjectivity that do not attempt to fit into an
outside, normalized concept of the human. Chapter four asks whether or not the type
of individual formed through health tracking technologies can operate within a larger
institutional setting. Where the previous chapters examine case studies of individuals
and their methods of self-care, chapter four traces the single case of how one particular
health-tracking service, 23andme, operates at the intersection of governmental/medical
institutions, the for-profit genome sequencing market, and individual users interested
in open source genetic databases. 23andme provides a particularly useful example of
self-tracking within the larger institutional landscape as its structure replicates the
tension between humanism and Enlightenment individualism present in the previous
chapters. The company relies on large-scale studies of genetic data to create a normate
model of the human for the user to compare itself against. At the same time, the
service also gives the individual information about their health along with some
guidance on how they can use the data to engage with critical self-care practices. It is
also this very tension – between access to medical data and the implication that the
user must create self-care practices around the results – that led the FDA to step in and
regulate the company. Within this dialogue between company, government, and
consumer, the issues of humanism and Enlightenment values identified in other
chapters play out on an institutional level.
23andme is a company that analyzes an individual’s spit for genetic markers
that could indicate particular traits, health conditions, or ancestry details. In 2013, the

16
FDA claimed that 23andme was a medical device and forced them to stop providing
their service, pending approval. Two years later, 23andme was cleared to provide the
test again, albeit with a limited range of reports. While many users look to this service
to get general information about their genetic makeup, many also share their data with
the hope of others using it for beneficial research. The tension here between
individuals wanting information, a company selling a product, and a governmental
agency attempting to establish regulations highlights a development in contemporary
medical technologies where humans no longer become local instances of diseases (as
in Foucault’s history of medicine discussed earlier), but become reconfigured as
capital through the storage, use, and re-selling of their genetic data.
This realignment of individuals with capital reflects Wendy Brown’s warning
that market rationality currently permeates social, governmental, and institutional
systems, reconfiguring individuals as capital and making the maximization of various
forms of monetary and non-monetary capital the primary goal of different spheres of
life.15 In terms of 23andme, this means gathering genetic data about a person to be
used in future studies to profit the company as well as creating users that are
concerned with investing in a future, healthy self. Brown claims that life ordered
around market rationality carries with it the removal of the promise of equality,
justice, and freedom that has come to be associated with democracy. She argues that
“the cultivation and expression of distinctly human capacities for ethical and political
freedom, creativity, unbounded reflection, or invention” get pushed aside as life

17
becomes an issue of winners and losers within deregulated marketplaces each trying to
enhance their position at the cost of others.16
The logic surrounding 23andme becomes significant because it provides an
instance thoroughly organized by market rationality and the idea of investing in
oneself to make a “better” person, but at the same time it actively encourages the types
of democratic activities that Brown worries about losing in an economically-organized
society, namely the ability to limit institutional power and the disappearance of a
platform of critique that allows instances of inequality and injustice to emerge.17 Yet,
the service does not point to an emergence of a utopian rule by popular sovereignty or
a return to homo politicus, where individuals are political beings. Instead, we see the
beginnings of an individual who utilizes information about their genetic makeup to
increase their own health-related capital while simultaneously publishing this
information online, putting themselves at risk for potential mis-use of their data for the
benefit of other individuals and the general population.
The process of configuring the individual as capital, but in a manner that does
not necessarily circumvent the promise of liberal democracy happens in several ways.
First, 23andme’s model revolves around providing information and guidance to the
user about how to engage with their data, but there is no clear, universal metric for
how the user can increase their capital in a way that can be relevant within a
marketplace. Finding out about particular genetic qualities allows a person to
understand more about how their bodies work and engage in practices of self-care, but
these findings are not always accurate or applicable outside personal development.

18
The second way in which genetic home tests configure the individual as capital is
through the governmental response to regulate the service on the side of the consumer.
Brown brings up a number of examples where neoliberal and market logic dictates
that governmental decisions play out typically in favor of corporations’ rights based
on principles of free speech. However, in the FDA’s case against 23andme, the
service was actually paused in order to put in proper regulations to protect the
consumer. The third way is an extension of this obligation to protect the individual.
Some users of 23andme have taken their data and published it online for anyone to use
for research or individual experimentation, putting themselves at great risk for future
mis-use of data for the possibility of helping others. Here, individuals do not become
isolated sites of capital accumulation at the expense of others, but rather act in shared
self- interest and capital accumulation. This chapter argues that 23andme may create
users, corporations, and governments that operate within a market rationality. But, the
relation between these entities actually creates a subject that opens up the possibility
for a renewed interest in the “ethical and political freedom, creativity, unbounded
reflection [and] invention” that Brown sees as lacking.
Overall, this dissertation attempts to identify a new way in which individuals
are using health tracking technologies to create localized versions of what counts as
human that disrupt some of the damaging tendencies of humanism to exclude those
types of individuals who do not fit the normate model of the human. These new
instances of “the human” rely on individual datasets and cannot be expanded in the
same ways as clinical medical knowledge to apply to populations as a whole or create

19
a normate version of what it means to be human. However, these models can create a
basis upon which others can engage in self-critical dialogue with their own data,
creating unique models of self-care that promote localized ideas of health. As shown
in the open source genetic data-sharing networks emerging around services like
23andme, there is also a significant community willing to put themselves at risk to
share their own data so that others may benefit. Here, in the decline of a universalized
notion of “the human” and the rise of a risky type of sharing, I hope to show that it is
possible to see the beginnings of a type of humanism – one that retains the idea of a
human in place of the human in order to re-invigorate Enlightenment ideals of
critique, justice, and ethics.
1
"Overview." Qualcomm Tricorder XPRIZE. tricorder.xprize.org. Web. 13 May 2016.
<http://tricorder.xprize.org/about/overview>.
2
Scanadu | Home. www.scanadu.com. Web. 13 May 2016. <https://www.scanadu.com/>.
3
Scanadu | Home
4
Foucault, Michel. The Birth of the Clinic; An Archaeology of Medical Perception. N.p.: New York,
Pantheon Books, 1973. Print.
5
Scanadu | Vitals. www.scanadu.com. Web. 13 May 2016.
<https://www.scanadu.com/products/vitals>.
6
"Wearable Technology - Statistics & Facts." Statista. www.statista.com. Web. 13 May 2016.
<http://www.statista.com/topics/1556/wearable-technology/>.
7
Garland-Thomson, Rosemarie. "Extraordinary Bodies: Figuring Physical Disability in American
Literature and Culture." New York: Columbia UP (1997). 8
8
Badmington, Neil. Posthumanism. Palgrave Macmillan, 2000. 3
9
Descartes, René. Key Philosophical Writings. Hertfordshire: Wordsworth Editions Limited, 1997. 107
10
Roden, David. Posthuman Life: Philosophy at the Edge of the Human. N.p.: Routledge, 2014.
11
See Foucault, Michel. The Birth of the Clinic and Foucault, Michel. The History of Sexuality. N.p.:
New York, Pantheon Books, 1978.
12
Chatterjee, JS. "From Compliance to Concordance in Diabetes." J Med Ethics 32 (2006): 509.
Also see Bissell, Paul, Carl May, and Peter Noyce. "From Compliance to Concordance: Barriers to
Accomplishing a Re-framed Model of Health Care Interactions." Social Science & Medicine 58 (2004)
and Campbell, R, M Evans, M Tucker, B Quilty, P Dieppe, and J.L. Donovan. "Why Don't Patients Do
Their Exercises? Understanding Non-compliance with Physiotherapy in Patients with Osteoarthritis of
the Knee." J Epidemio Community Health 55 (2001) for other, very similar, arguments in favor of
concordance.
13
Quantified Self | Self Knowledge Through NumbersQuantified Self | Self Knowledge Through
Numbers. quantifiedself.com. Web. 13 May 2016. <http://quantifiedself.com/>.
14
Rabinow, Paul, and Nikolas Rose. "Biopower Today." BioSocieties 1 (2006): 197.
20
15
Brown, Wendy. Undoing the Demos. N.p.: Duke Univ Press, 2015. 31.
16
Brown 43
17
Brown 208

CHAPTER 1
Reclaiming the Human in Posthumanism
In the early twenty-first century, the integration of human and machine has
become increasingly commonplace, bringing renewed interest to the boundaries of the
human. People with failing hearts get pacemaker implants, individuals with bad
eyesight undergo Lasik eye surgery to correct their vision, the hard of hearing can get
cochlear implants to improve their auditory senses, and broken bones are enclosed in
custom-printed 3D casts. On the other end of the spectrum, humans use technology to
improve their own ways of functioning. Extreme examples of bodily enhancement are
“grinders” – people who “hack” their body and install various DIY implants into their
bodies. One such implant is a neodymium magnet placed on the pads of the fingers
that allows the individual to feel surrounding electromagnetic fields, such as
microwaves or surrounding magnets.1 Another is an RFID (radio frequency
identification) chip that emits a unique signal and can be used to unlock electronic
devices such as computers.
These medical operations, among countless others, present a unique transition
whereby computers or other electronic sensing devices are introduced into the human
body to expand the ways it can work and sense within the world. By incorporating
technology into the body in this way, contemporary use of technology is calling into
question a long-held division between the human and machine that, unlike previous
versions of this critique, looks at machines not just as objects without consciousness,
21

22
but as potential agents for creating new forms of consciousness and possibilities of
interacting within the world.
Where advocates of these new technologies see a utopian world where the
human can be fixed or improved through technology, many scholars see these
technologies as deeply problematic, at best advocating a failed vision of leaving the
body behind and, at worst, reinscribing power structures that disempower and exclude
individuals who do not fit the appropriate type of human. These scholars, generally
grouped together under the title of “posthumanists” – or more specifically, critical or
cultural posthumanists – provide a critical examination of technology that is able to
take into account cultural, social, ethical, and ontological issues surrounding the
introduction of new technologies.* Posthumanism’s ability to approach these topics is
couched in a belief that the primary quality of “the human” has, for centuries, been
understood to be heavily skewed toward the Western, rational, white, male subject,
which marginalized groups such as women, non-Western cultures, individuals with
particular disabilities, and non-rational modes of thought. Posthumanism looks to
contemporary technologies as a way to show both the previous assumptions which
have been tied to the human as well as identify possible ways that these technologies
allow those assumptions to be reconfigured within new subjectivities. By creating
legitimate forms of subjectivity outside of what has traditionally been called “the
*
The type of posthumanism that I will be discussing concerns what is commonly termed critical or
cultural posthumanism. This particular type of posthumanism stands opposed to the posthumanism of
thinkers like Fukuyama who see posthumanism as meaning post-human and examine what a new, non-
human person would look like. For more information on the differences between the types of

23
human,” posthumanism attempts to create an ethical engagement with these formerly
marginalized groups and legitimize them in legal, social, and cultural realms.
However, it is necessary to note that posthumanism should generally be
understood as post-humanism, not post-human. In attempting to open up the human
for different modes of subjectivity, many forms of posthumanism end up advocating
for a different type of human, not a wholesale rejection of it.2 The exact ways that this
occurs will be examined below, demonstrating that the overall hope of posthumanism
is to create a type of subjectivity that affords the possibility of multiple configurations
of the human, which in turn devalue the Western, rational, white, male subject
position. This chapter will provide an overview of posthumanism as a project of
critique of the rational subject arising from humanism that is deeply involved in
redesigning ethical considerations in the twenty first century. The following chapters
will take up these theories of posthumanism in relation to medical technologies – an
area that has been deeply embedded in generating the figure of the human since the
rise of clinical medicine in the eighteenth century – to show how contemporary
medical technologies are able to retain a constant critical engagement of “the human”
while also promoting ethical engagement with others.
The form of humanism that provides a basis for posthumanism began to take
hold as the dominant Western conception of the subject in the 17th century. During
this time, thinkers such as Descartes began to posit the existence of a type of core
posthumanism, see Miah , Andy. “Posthumanism: A Critical History” in Gordijn, B. & Chadwick, R.
(2007) Medical Enhancements & Posthumanity. New York: Routledge.

24
humanity, a particular essence that created an entity that could be designated “the
human” or “Man.” For Descartes, this essential human characteristic was reason,
which gives both the power of judgment as well as the ability to tell the human from
the non-human.3 Identifying reason as a uniquely human characteristic served to create
a boundary between human and non-human. The human became that which possessed
reason and the non-human became that which did not. The non-human included
inanimate objects such as trees, rocks, houses, or any number of other objects. It also
included organic entities such as animals that appeared living, as humans did, but
could not rationalize. Using rationality to draw a line between Man and non-Man,
Descartes and subsequent humanists started to isolate the human as a subject that did
not rely on these lesser, non-reasoning forms to exist. Consciousness and rationality
were their own entities and could be studied independently of outside factors like
physical surroundings, culture, and society, .
At times, the appearance of rationality could emerge in other objects, most
notably the animal and the machine. Descartes claimed that animals appear living
because they sometimes exhibit speech, as in the case of a parrot or a monkey that
communicates ideas with its species, and have a certain amount of dexterity in certain
tasks.4 However, animals cannot communicate their thoughts to humans, nor do they
surpass humans in performing all types of tasks. Thus according to Descartes, “they
have no reason at all. It is nature which acts in them according to the disposition of
their organs, just as a clock, which is only composed of wheels and weights, is able to
tell the hours and measure the time more correctly than we do with all our wisdom.”5

25
For Descartes, the animal is not human because it is mechanistic and cannot reason on
its own, instead operating on instincts and reactions that do not require introspective
thought. Indeed, Descartes claims that if an automata were created that looked and
acted like an animal, “we should not have had any means of ascertaining that they
were not of the same nature as those animals.”6
Like animals, machines for Descartes may give off the illusion of human-ness,
but they are not able to truly reason or think critically and, thus, are not truly human.
If humans were to encounter a machine masquerading as human, they would be able
to note two things that betray the machine: (1) its incorrect use of language and (2) its
inability to outperform a human in every task, even though they may do better in
some.7 In each case, the machine gives itself away because it does not always act as a
rational being, even if it initially appears that way. Though Descartes was referring to
seventeenth century automata, contemporary examples underscore his points clearly
as well. For example, Apple’s Siri program comes installed on all new iPhones and
allows the user to interact with the phone’s operating system by asking questions or
giving voice commands. Siri can understand natural language, which allows the user
to speak as they would to any other person, rather than being restricted to certain
preset commands. Most of the time the program works well, answering the user’s
questions or providing the data requested. Sometimes, however, Siri mis-hears the
command and provides something entirely different than what is asked for, or cannot
perform a task because it is not programmed to do so. When this happens, Siri’s
limitations as a machine are glaring. In a more extreme example, a machine such as a

26
blender may chop up food much better than a human might, but it can’t play chess to
the same degree or work out complex mathematical equations.
Placing reason as the centerpiece for the determination of the human also
brings the mind to the forefront. In opposition to the mind, the body exists “as a
machine which, having been made by the hands of God, is incomparably better
arranged, and possesses in itself movements which are much more admirable, than any
of those which can be invented by man.”8 The body itself becomes linked with the
non-human “machine,” capable of only performing pre-programmed movements and
actions. The human body may be a better machine because it is created by God, but it
is still subject to its natural needs (food, water, sex, etc.), unlike the mind that can
think for itself through rationality. For Descartes, the body may be a part of a human
body, but it is a part that is not integral to the formation of the human. Because the
rational mind develops independently of the body and, often, is distracted by the
natural needs of that body, the body is something that stands in opposition to a
rational human.
This focus on the rational mind as the locus of the human creates a subject that
may be encapsulated within a body, but is constantly trying to reach beyond that body.
The body encasing the mind as well as the outside world full of non-human objects,
animals, and machines are all encountered by the subject, but they do not constitute it.
This opposition is the boundary of the human: the human is “human” because it is not
an animal and not a machine. Defining the human in this manner gives rise to a series
of oppositions such as subject/object, rational/irrational, wild/tame, etc.9 Many

27
examples of this division do indeed create a distinct line that allows the human and
nonhuman to appear completely separate. A doctor, for example, tends to possess
reason and operate much as we understand a “human” to, while a toaster can hardly be
said to possess reason.
The emergence of humanism during the Renaissance set the stage for
humanism’s role in the Enlightenment, which followed shortly thereafter over the
course of the seventeenth and eighteenth centuries. The parallel existence of
humanism (a mode of thought) and the Enlightenment (a historical period) resulted in
an important turn in thought that would last for the next several centuries.10 On the one
hand, the Enlightenment privileged liberation, justice, and actions that came from
one’s own choices and opinions. Humans should use their rational skills to liberate
them from fear and oppression.11 The Enlightenment saw the rise of new political,
social, and philosophic ways of thinking that focused on the benefits of rational
thinking and scientific exploration into the workings of the world. By implementing
rational and scientific projects, Enlightenment thinkers were able to make apparent
progress toward the ideals of “justice” and “freedom.” Writing in the late 1700’s and
reflecting back on the intellectual movement, Immanuel Kant characterized the past
centuries as “man’s emergence from his self-incurred immaturity,” meaning “the
inability to use one's own understanding without the guidance of another.”12
Kant’s move emphasizes that the important aspect of being human comes not
just from the possession of rationality in general, but an individual’s expression of that
rationality unswayed by any outside influence. Requiring that the individual use its

28
own rationality to critique the world results in an ideal type of subject that is
autonomous and should act without any outside cultural, social, or institutional
interference. With a proper maturing and use of reason, Kant claims that humans will
be free. By this, he means a “freedom to make public use of one's reason in all
matters.”13 Here, it is possible to see an expression of the humanist subject as a
potential solution for the Enlightenment problems of justice and freedom through its
ability to think on its own and the organization of society in a way that allows for an
individual’s public use of reason without fear of punishment.*
Kant’s elision between Enlightenment ideals and humanism introduced a
significant change into the way that humanism operated – and continues to operate –
by orienting it around anthropocentrism. Kant’s thought has been characterized as a
type of “transcendental humanism” which put forth the idea that the primary
organizing principle of the world is the human mind, which actively imbues the world
with value, form, and meaning.14 Here, the human is not just the only entity capable of
rational thought, but the very origin of the world itself – a divine being. This idea
stood in contrast to the earlier humanism of thinkers such as Descartes that posited a
rational and human-independent world governed by mathematical laws and left space
for a non-human God. Kant became the turning point for a type of humanism that put
*
The heightened sense of individualism will be examined in more detail in the following chapters as a
complicated and paradoxical force within the humanism/Enlightenment way of thinking. Chapter 2
demonstrates that among patients with chronic diseases, the push toward individual responsibility
started as a way to internalize medical procedures and a certain type of subjectivity, but then actually
worked against reproducing a particular medical subject by allowing individuals to make choices that
sometimes go against doctor recommendations. In Chapter 4, individualism will be seen as a mode of
thought tied with the extension of neoliberal free market principles to everyday life, affecting the ability
of individuals to engage within the political sphere.

29
the human completely at the center of philosophical thought.15 This radical
anthropocentrism continued through philosophers influenced by Kant, including
Hegel, Husserl, Heidegger, and others who make claims that “identify the conditions
of possible knowledge or meaning with facts about human subjectivity.”16 For these
thinkers, an understanding of a noumenal world is not possible. We are limited only to
the concept of reality that we can know and access as humans.17 This radical
anthropocentrism also becomes the focus for numerous posthumanist critics, who
seek to decenter the rational mind as the main organizer of the world.
One of the initial moves in decentering the human was to position humanism
not as a natural construct that accurately reflected reality, but as culturally, socially,
and historically situated. Nietzsche was one of the first to claim humanism as an
empty concept that did not objectively reflect reality, while critics like Foucault,
Gramsci, the Frankfurt school, and psychoanalysts all worked to undo the authority of
humanism in the late twentieth century in different fields.18 “Man” or “the human”
came to be recognized not as a fully formed being to be discovered or a particular
entity that had internal unity that science and philosophy helped to discern or identify.
Nor was Man the transcendental subject that created the world, as in Kant’s
humanism. Rather, Man was an idea or a “figure of speech” formed through epistemes
that constructed him, notably the Enlightenment and its focus on reason. Dangerously,
this figure did not herald the age of justice and ethical consideration for others that
Kant and Enlightenment thinkers had hoped, but rather served as a historically-,
culturally-, and socially-specific figure that could be used in processes of exclusion.

30
Often, justice and freedom became issues for individuals who straddled the
line between human and non-human, according to the precepts of humanism.
Examples that blurred the line between human and nonhuman posed ontological and
bureaucratic questions as to what being “human” entails and who could be the
recipient of justice and freedom. For instance, a human-looking body with a non-
rational or “brute” mind is one of these blurred boundaries as it appears biologically
human yet does not meet the qualification of possessing reason. One such historical
example is hermaphrodites who were considered criminals because they could not be
clearly classified as man or women.19 Such a configuration could not easily be
reconciled with laws regarding marriage and unions between individuals that relied on
the strict male/female designation, resulting in the hermaphrodites being outside of
bureaucratic protection. Aside from sexual variations, requiring humans to have both
a body that appears human and a rational mind resulted in a problematic
characterization of individuals with mental disabilities or less “civilized” ways of
socializing. These individuals were labeled non-human because they do not conform
to a pre-determined idea of what it means to be “reasonable”. Identifying different,
“proper” characteristics in order draw a boundary around the human results in
oppressive power structures that normalize certain behaviors and qualities. Different
forms of “reason,” configurations of the body, or ways of being are pushed aside for a
regime of reason that is actually historically situated and subjective rather than, as it
claims, completely objective and reflective of some type of human essence.

31
The intersection of law and medicine were the primary ways that this type of
exclusionary humanism was enacted. Law identified a type of model citizen that,
along humanist lines, would be rational and knowable to themselves. This, combined
with Enlightenment individualism, created a type of person that was culpable for their
actions and, as a result, could be charged with crimes. If a person transgressed the law
knowingly, they deserved the punishment handed down by the law. Foucault provides
an example of this intersection between humanism, law, and medicine in the case of
Henriette Cornier. Cornier was a house servant who, in the early nineteenth century,
killed her neighbor’s infant daughter in a calm, premeditated manner.20 The ensuing
trial revolved around whether or not Cornier was in possession of reason when she
carried out the act. Though she appeared to be in control of her senses and in
possession of a rational mind throughout the murder, as evidenced by her planning
and demeanor, she also did not appear to have a motive. Additionally, she did not
appear to have the qualities typically associated with dementia or hysteria. She
appeared mad, having no reason for her action. This creates a difficult situation that
the law was not poised to deal with. Cornier appeared both reasonable and un-
reasonable at the same time, requiring the law to be applied but without a justification
for being exercised.21 The law had to turn to an outside authority to provide a
justification for the exercise of punitive power (she had a particular motivation for
performing her act) or a rationale for not acting (she was, indeed, demented).
Classifying the act as mad, as outside the bounds of legal or medical explanation,
could not be tolerated because it had no corresponding legal action. Psychiatry was
brought in to classify Cornier as subject to

32
a “barbarous instinct.”22 This “barbarous instinct” partially attempts to bring back in
delirium as an explanation for Cornier’s acts, but only because it has not yet fully
been formulated through psychiatry. Over the course of the next century, “instinct”
becomes “a whole domain of new objects” that “are impulses, drives, tendencies,
inclinations, and automatisms. In short, they are all those notions and elements that, in
contrast with the passions of the Classical Age, are not governed by a prior
representation but rather by a specific dynamic in relation to which representations,
passions, and affects have secondary, derivative, or subordinate status.”23 Transferring
“madness” into “instincts” allows psychiatry, and the penal system it is intertwined
with, to exert a certain amount of control over acts that seem to lack reason. There
may not have been a conscious motivation for the acts, but there was an identifiable
system, presented by psychiatry, that could make sense of the acts and put them in a
logical pattern which could be understood by authorities. The “mad” act or the
madman is no longer outside the purview of the reason-based legal system through the
justification of the medical field, allowing the act (and the person performing the act)
to be legible to the law and able to be tried in a court of law.
By bringing together the application of law and medical assessment of
patients, Foucault was able to identify a type of logic at work that created a “normal”
idea of the human. Chapter 2 will look into detail as to how the medical field changed
throughout the eighteenth century, but for the purposes of laying out a framework of
posthumanism the most important point is that the philosophic underpinnings of
humanism have not been only theoretical or philosophical, but have created a type of

33
logic that has be integral in the formation of medical and governmental institutions.
For many scholars these restrictions and the broadening of control to encompass
aspects of citizens’ lives represent some of the more nefarious results of humanism.
The abnormal citizen cannot be tolerated within a humanist-based society, requiring
control apparatuses to be put into place that produce a particular subject who regulates
themselves in particular kinds of socially acceptable ways in accordance with certain
norms. As a result, the posthumanist critique of humanism centers around not
critiquing the existence of the human for its own sake, but in trying to move beyond
radical anthropocentrism in order to deal with these issues of exclusion and ethics that
present themselves as effects.
One of the ways that this critique occurs is a shift from focusing on the
particular qualities of what made up the “human” toward a concentration on the
technological milieu that the subject found itself in and created itself out of in an
attempt to identify the forces behind process of exclusion.24 The subject no longer
constructed itself on the basis of an inherent rationality or a higher-order human
processing ability that separated it from other living entities and inert objects. Instead,
the subject was constructed hermeneutically and culturally from technologies that
would express a certain way of being. The subject was one that emerged out of
technology and held no inherent unity outside of its historical position. What counted
as a “fully formed” and ideal human changed over the course of years, removing the
possibility of finding any sort of distinctive, immutable essence. The task of
posthumanist critique became to pull apart what the figure of the human was at any

34
given point and shed light on the assumptions and predispositions that went along
with it. The hope was that by performing this critical action, new forms of subjectivity
could emerge that would work against oppressive power structures.
The field of critical (also known as cultural) posthumanism began to emerge in
the late twentieth century in response to a particular historical moment happening
parallel with the greater critical attention to humanism that started with Nietzsche.
Whereas automata had been a site of concern for humanism since the time of
Descartes, mid twentieth century investigations into artificial intelligence began to
reinvigorate framings of human consciousness into completely rational terms,
specifically so they could be reproduced within a computer. Here, it is possible to see
the beginnings of an attempted elision between man and machine that had previously
been a hard boundary. As technological development moved to replicate the human,
utopian visions of man/machine hybrids that improved on the initial human character
emerged, putting aside the autonomous self that originated with Descartes.25 The
humanist framework runs into issues when reconciled with contemporary technology
that either replicates rationality without a body (as with cybernetics and artificial
intelligence) or combines man with machine (as with the concept of the cyborg in
science fiction). By trying to reverse engineer the human as a computer, AI
researchers continued the search for a type of human essence that could be
reconstructed in electronic form. In doing so, they created new types of subjectivities
that have been the basis for critical posthumanism.

35
Called “transhumanism,” this mode of thought tries to amplify human qualities
and make them better through integration with technology. Transhumanists hope that
technological innovation will add to “the limited toolkit of traditional humanism” by
extending the human beyond its “natural” limitations26. As a result, the humanist
values of reason and autonomy could be made more prominent, essentially becoming
“better” individuals by becoming more rational humans and making stronger, healthier
bodies through the use of contemporary technologies.27 Just as it tries to do away with
the ailing body and imperfect human form, transhumanism ends up solidifying many
of the centuries-old discourse surrounding what makes up the human. The ultimate
goal is to leave the human body behind and replace it with a technological one. Such a
feat would only be possible if – in a very humanist manner – the only identifiable
element of the human was consciousness and rationality, and not the body that housed
it. These are the grinders and self-experimenters such as Kevin Warwick mentioned
above.
Transhumanists often support the idea of “downloading consciousness” into a
computer, an idea championed by researcher Hans Morevac in his book Mind
Children and perpetuated by thinkers such as Ray Kurzweil.28 According to Morevac,
Kurzweil, and other transhumanists, it is possible to identify the underlying
organization of thought and create a computer that mirrors that organization. With
enough computing power and enough storage space, it would then be possible to scan
the human mind and move it into a computer, much like copying a CD or a file.

36
Yet Kurzweil and many other transhumanists still retain hope that
consciousness will eventually be able to be transferred to a machine. By modifying
their own body – or doing away with it entirely by moving consciousness into a
machine – and making it “better,” transhumanists hope to move beyond the limitations
of the human body in order to isolate the elements of rationality and self-knowledge
away from the faulty operations of the body that cause it to decay or be bounded
within its own skin. Often for transhumanists, a “better body” means one that cannot
die.*
Ironically, the endgame of transhumanism is not necessarily a good solution
for humanists who privilege Enlightenment values of autonomy and individualism. At
the extreme end, integrating consciousness into computers would create a collective
intelligence, much like the Borg on Star Trek, and eradicate the ability of a human to
work as an individual.29 Becoming “more human” in the liberal humanist sense that
requires a unified, self-knowing individual is less possible within this scenario, as the
ability to replicate consciousness and share information easily erases the borders
between individuals. Within the transhumanist ideals, rationality remains central but is
not necessarily coupled with a unique and autonomous individual or the celebration of
a diverse and culturally rich population. Issues of ethics and justice are less important
here because the population is homogenous, sharing a single hive consciousness.
*
An argument could be made here that removing the ability to die would also radically change our
subjectivity. Existential thought and Heideggerian phenomenology both focus on how orientation
toward death organizes our being. If we were to take away that ability to die, it would follow that how
our being is organized would be changed in a way even more drastic than if we were to take away or
change our bodies.

37
Utopian techno-fantasies such as those advanced by Morevac and Kurzweil
occurred (and are occurring) alongside bodily-centered advancements in technology
(prosthesis mentioned above, as well as health tracking technologies addressed later in
this dissertation) and a critique of humanism. Where transhumanists see these as
potentially creating better humans, scholars like Katherine Hayles, Neil Badmington,
Donna Haraway, and others take these discourses as the flawed start of a possibly
liberating move away from the figure of the human in general. The transhumanists’
desire to shed the body is impossible and a dangerous argument for homogeneity, but
it does point to a malleability of the body and identity connected with contemporary
technologies that move beyond the figure of the human championed by humanism.
While critical posthumanists (and the off-shoots of Object Oriented Ontology
and Speculative Realism discussed below) push for a radical anthropocentrism that
looks for alternative subjectivities and non-human ways of being, I will argue
alongside critics like Braun, Halliwell, and Mousley, that posthumanist discourses are
actually “humanisms with a vengeance” that reproduce the figure of the human.30
Even the aggressively anti-anthropocentric Object Oriented Ontology and Speculative
Realism do not deny the existence of human consciousness, only deny its primacy.
However, far from being just a failure of posthumanism to achieve its goal, I claim
that posthumanist discourses are able to reconfigure the human in a way that separates
Enlightenment goals of ethics, justice, and critique away from needing a universal
figure of Man as a referent. In this way, the anti-anthropocentrism of posthumanism
can be read not as not a project to destroy any sort of human figure, but to move

38
toward creating a subject that occupies multiple identities and subject positions in
order to promote ethical engagement with other individuals.
As a type of proto-posthumanist, Donna Haraway anticipated and influenced
the critiques of later posthumanists in her feminist critiques of humanism.* For
Haraway, humanism works through aligning itself with an apparent objectivity within
technology and science that covers over the “unmarked positions of Man and White”
propagated through these discourse.31 The rational, unified, and universal figure of
Man that humanism advocates is shown in her work to be deeply and problematically
gendered and racialized. To combat the exclusionary figure of Man, Haraway
advocates for an identity politics based on the figure of the cyborg, a schema that has
provided the basis for other posthumanist thinkers.
For Haraway, the cyborg erases the boundary between human and machine.
Not only does this move beyond the strict humanist divide between man and machine,
the ability to integrate technology into the body allows the human body to expand
beyond itself into the surrounding environment. As she claims in later works, moving
beyond the concept of the human that appears objective (while still being distinctly
male and white) involves understanding the body as situated and connected to
surrounding environment and technologies.32 By embracing this situatedness,
interaction, and changeability through prosthesis and body extension, it is possible to
*
Haraway ardently claims that she is “not a posthumanist” (When Species Meet 19), but her work is
often referenced by posthumanist scholars. Moreover, in the same work that she denies her allegiance to
posthumanism, she claims that she does have “posthumanist whisperings” in her ear (73). For the
purposes of this chapter, it is less important to figure out definitively whether Haraway herself claims to

39
create new forms of human subjectivity that can be used to advance different
configurations of gender and race.
Without relying on a single, unified state (as in more traditional humanism),
Haraway’s cyborg is free to constantly reconfigure its identity and self through its
situatedness within a particular environment. Without a concrete identity or a single
ideal configuration of the human to work toward, there is also no “myth of original
unity, fullness, bliss and terror, represented by the phallic mother from whom all
humans must separate” that allows the cyborg to emerge.33 This original myth in the
humanist tradition is the moment at which the subject becomes an individual,
autonomous, rational being that is, at the same time, always white and male.
Haraway’s call to recreate identity politics and dismantle gender norms gets
pulled into other posthumanist projects that emerged in the 1990s. Katherine Hayles is
one of the most prominent posthumanists. She in particular has targeted
transhumanism as a potentially dangerous über-humanism for the similar reasons that
Haraway has identified in traditional humanism. In her book How We Became
Posthuman, Hayles outlines the general principles of the posthuman* (what I have
above termed “transhumanism”):
First, the posthuman view privileges informational pattern over
material instantiation, so that embodiment in a biological substrate is
seen as an accident of history rather than an inevitability of life.
be a posthumanist and more important to understand her influence on and engagement with
posthumanist thinkers.
*
Note that here – and throughout her book - Hayles uses the term posthuman to denote discourses and
practices that attempt to create a new, better human through technology and prosthesis. I’ve used the
term ‘transhumanism’ to make the opposition to posthumanism more clear. Hayles, Haraway,
Badmington, etc. all are critical of transhumanist/posthuman claims and goals, but see positive
possibilities in developing posthumanism.

40
Second, the posthuman view considers consciousness, regarded as the
seat of human identity in the Western tradition long before Descartes
thought he was a mind thinking, as an epiphenomenon, as an
evolutionary upstart trying to claim that it is the whole show when in
actuality it is only a minor sideshow. Third, the posthuman view thinks
of the body as the original prosthesis we all learn to manipulate, so that
extending or replacing the body with other prostheses becomes a
continuation of a process that began before we were born. Fourth, and
most important, by these and other means, the posthuman view
configures human being so that it can be seamlessly articulated with
intelligent machines. In the posthuman, there are no essential
differences or absolute demarcations between bodily existence and
computer simulation, cybernetic mechanism and biological organism,
robot teleology and human goals.34
These views fit very much in line with the transhuman tenants above that seek to
improve on the human condition by augmenting it with technology. However, these
transhumanist/posthuman projects have not yet been realized, nor do they accurately
portray the differences between AI and embodied, environment-dependent human
consciousness. The transhumanist belief in moving consciousness from human mind
to machine requires a belief that “mental states…are substrate-independent” and could
exist in “arrangements of matter very different from human bodies.”35 It is the very
arrangement of body, consciousness, and surrounding environment that allows “the
human” (or what appears to be the figure of the human) to emerge. Changing the
arrangement would result in a much different type of subject, if not erase the
possibility of subjectivity entirely. For transhumanists, this would be a failure of their
project to create a better human.
The types of technologies utilized in transhumanist projects do, however, have
liberating potential. Even as she warns that we must not forget the body, Hayles points
to the devaluation of the body within contemporary technological discourse as a move

41
that also opens up the potential for types of identities that do not fit into the normate
model of the human as long as we remember to include materiality within critical
analysis.36 Reconfiguring identity as a fluid consciousness that does not depend on
rationality or a stable embodiment pushes aside the autonomous liberal subject of
humanism that exists opposite and apart from an anthropocentrically ordered world of
objects. As a result, the posthumanist subject becomes embedded within the world and
is no longer entirely distinct from that world, nor is it the transcendental subject of
Kantian humanism.37 Human agency becomes the ways that consciousness can move
within, order, and interact with these surroundings rather than its ability to cut itself
off from its surroundings to engage in autonomous rational thought and order the
world, as in Kant.
Critics of posthumanism have latched on to this inability of posthumanism to
completely forego identity and the human as a central talking point. They argue that
posthumanism ends up less a complete break from humanism and more of a
rearticulation of humanism. Scholar Bruce Braun writes:
What often goes unnoticed is that by historicizing the posthuman we
end up recentering the human: the human is that being that `once was',
but which has been `eclipsed' or `transcended'. Here's the crux: such
posthumanisms require the figure of `Man', and in so doing, become
humanisms with a vengeance, for they produce as a historical fiction
precisely that which they imagine to have left behind. In this sense,
posthumanism's fevered celebration of the posthuman is of a kind with
humanism's mourning of the passing of `Man'. We must ask, then,
whether our posthumanisms have themselves become `anthropological
machines', unwittingly accepting the same story of the human and its
passing…, merely coding positive what they code negative?38
Braun makes a point that is backed up by Hayles, Badmington, Derrida, and others
that if we look at posthumanism in the context of how it arose, we see that

42
posthumanism not only must build off of the idea of the human initially constructed
by humanism, it must also keep that idea of the human generally in tact.39 To allow
the human to extend beyond the body and to become completely entwined with
technology in new ways of being, there must be an idea of “human” to start with.
Similarly, the body is not necessarily completely sloughed off, but rather extended and
added to by means of prosthetic extensions. Hayles observes that posthumanism can
become dangerous in this manner because posthumanism’s extension or amplification
of the liberal humanist subject carries with it the possibility of replicating power
structures bound up with that type of subjectivity.40 The type of subject privileged
through humanism is a subject with autonomy and rationality. As in Descartes’
framework, there is the threat of individuals lacking that rationality being excluded
from the category of the human, thus removing any sort of ethical obligation toward
them. In posthumanism, if the rationality and autonomy of the humanist subject is
enhanced through its encounter with technology rather than completely re-worked, it
carries the same danger toward those who do not meet the normative requirements of
being a humanist subject.
However, I would argue that the goal of posthumanism is not to put aside the
figure of the human for its own sake, but to dismantle the power structures that
emerged from humanism that are largely dependent on a stable, universal figure of the
human. Critical posthumanists take on the multiplicity and situatedness of
consciousness to create fluid identities that work against universal constructs of the
normate human. If anything, posthumanism brings to the forefront latent anti-humanist

43
ideals present within humanism itself41. Halliwell and Mousley in particular have
analyzed humanism not as a monolithic, singular set of ideas but as a multiplicity of
different strains that often act in a self-destructive and paradoxical manner. These
include subsets such as the “romantic humanism” of William Shakespeare, Karl
Marx, and Helene Cixous that does not automatically discard feeling for a focus on
reason; the “civic humanism” of Mary Wollstonecraft, Jurgen Habermas, and Stuart
Hall that identified citizenship as the underlying essence of humans; and the “spiritual
humanism” of Walter Benjamin, Martin Luther King Jr., and Julia Kristeva that
retained the relevance of God within the need for humans to come into their own.* For
them, humanism and anti-humanism are part of the same structure, one that can be
saved from irrelevance and potentially dangerous situations by focusing not only on
the question of what comprises human essence, but by focusing on the critical and
self-critical spirit of humanism. Humanism contains within itself the seeds of its own
self-reflection that has presented a series of problems and issues beyond just
attempting to locate reason as the single important aspect of the human.
The critical humanism of Haraway and Hayles attempt to position the subject
as malleable and situated in order to open up possibilities for gender and race, but
more recent scholarship has looked at examining the situated aspect of
posthumanism. Object Oriented Ontology and Speculative Realism both seek to
create an ontology of
*
Halliwell and Mousley include a number of other specific types of humanism that include anti-
humanist elements. It is also worth noting that the thinkers that Halliwell and Mousley place into these
categories are not always strictly traditional humanists. For example, Foucault, Baudrillard, and
Haraway are included in a “technological humanism” section, though each author could easily fit into a
posthuman or anti-human model. For Halliwell and Mousley, this fluidity of categorization is precisely

44
objects and move away from anthropocentric discourse. The primary goal here is not,
as with the critical posthumanism of Haraway and Hayles, primarily a feminist
project, but rather an attempt to not get stuck re-articulating humanism and re-
asserting it as the only form of ontological investigation. Even so, Object Oriented
Ontology and Speculative Realism can potentially open up ethical dimensions not
covered in the critical feminist posthumanism.
To move beyond a human-centered approach to theory, Speculative Realists
argue that rather than continuing with critical posthumanism’s textual deconstructions
of subjectivity, anthropocentrism can only be undone by shifting philosophical
concern away from subjectivity and toward the “cosmic throng of nonhuman
things.”42 Such a move operates in direct opposition to the transcendental humanism
of Kant that places the human as the organizer of the world and Descartes’ humanism
that positions consciousness as the only certainty. For OOO and Speculative Realism,
objects outside of human consciousness can also organize the world in particular
ways, creating a space for non-anthropocentric subjectivity. Notably, this change in
thinking comes with a focus on “intentionality.”
The problem of intentionality began as a way to deal with one of the major
side effects of the Cartesian identification of “human” and “non-human.” Humans, for
Descartes, possessed rationality, which became identified with consciousness, or the
Cogito. Non-human elements were located in the world or reality, apart from the
rational, conscious Cogito. The relation between the human and non human posed an
the point. They are attempting to make the claim that humanisms and the resulting anti-humanisms are

45
issue and following this Cartesian split, two strains of thought emerged: realism and
idealism. Realism claimed that the world was primary and that our experience of
objects outside our consciousness reflected how those objects actually existed.
Realism became problematic when dealing with more abstract concepts like morality,
agency, sensation, and illusion. Idealism, however, claimed that our experience of the
world was entirely created by consciousness and that access to any sort of “true”
reality was called into question. This strain of thought worked well with addressing
the abstract concepts that realism could not handle, but had difficulty justifying a
shared world of experience and objects among different people.
In response to some of the issues stemming from the hard division between
realism and idealism, phenomenology emerged, bringing with it the idea of
intentionality. Beginning with Husserl, phenomenology called into question both the
concrete existence of a world outside of consciousness and the privileging of
consciousness as the creator of its own experience. Through a re-investigation of how
consciousness operates, Husserl found that even without assuming a “real” world
outside consciousness, there were still phenomena that presented themselves to
consciousness. Moreover, consciousness did not exist without being directed toward
that phenomena. “Intentionality” is Husserl’s term for this directedness of
consciousness toward objects in the world. Through intentionality, the
phenomenological subject organizes consciousness and the world, but in a way that
still allows for the existence of outside objects. For Husserl and other
all part of the same system and are much more complicated than a simple dialectical opposition.

46
phenomenologists, intentionality points to the interconnectedness of consciousness
and the world while also incorporating the notion of a continued, constantly changing
living within this world. Consciousness cannot be created without the encounter with
some sort of phenomena that exists outside of it, within a world. Likewise,
intentionality gives meaning and shape to objects within a world, which otherwise
could not exist as anything recognizable as a “world.” This intentional relation is
constantly being acted out as “lived reality” as phenomena present themselves to
consciousness and consciousness intends toward them.*
Within this phenomenological structure, technology occupies a unique
position. Though many forms of technology could be said to be “in the world” (to be
objects that are presented to consciousness) they also, to a degree, change how other
objects within the world are presented. Heidegger was one of the first to address this
issue with his discussion of tool use in Being and Time. He describes the use of a
hammer, pointing out that we become unaware of the tool itself as long as it is
working and performing the function we are attempting to use it for. In this process,
the hammer becomes what he calls “ready to hand.”43 For Heidegger, because we are
not focused on the physical tool itself when it is working properly, the tool is actually
incorporated into consciousness and affects how we intend the world. We begin to
see things as things to be hammered (nails, rocks that should be broken apart, metal
that
*
As Verbeek points out in {Verbeek 2005 @ 109-110}, the focus on interrelation between human and
world is characteristic of later phenomenology, while classical phenomenology is more aligned with a
philosophy of consciousness. Again, it is not my intent to give a full history of phenomenology here,
but rather to identify the main issues that are later taken up by postphenomenologists and philosophy of
technology.

47
needs to be pounded into shape) or not to be hammered (screws, glass cups, antique
vases). If we were to change tools, our experience of the world would change as well.
A level, for example, would cause objects we encounter to be put in terms of how
parallel to the ground they are (or are not) and do little to draw our consciousness
toward the hammerability of particular objects.
Heidegger later expanded this analysis of tool use to point out that technology
changes the way in which the world is revealed to us in general, not just when we are
specifically using the tool. In his essay “The Question Concerning Technology,” he
makes the claim that modern technology such as hydroelectric plants causes us to see
the world as a “standing reserve” of resources that we can uproot and use for our own
purposes. It is not important to identify whether this is an accurate description of how
modern technology shapes the world for us; it is useful only in so far as it draws
attention to how it is one of the first moves in phenomenology toward describing
technology’s affect on consciousness’s essential experience of the world. We do not
see the world in terms of standing reserve only when we are actively engaged in using
the hydroelectric plant as something ready to hand. We constantly see the world in
terms of standing reserve because we are constantly engaged with a type of technology
that causes us to view the world in this manner.
For Heidegger, the primary question is how to understand how the tools affect
the being of the human, or Dasein. As Graham Harman, Ian Bogost, and other
Speculative Realists have pointed out, this leaves out the question of the being of the
tool itself.44 The tools in Heideggerean thought are only important in so far as they are

48
part of a situation involving a person. In the above example, the hammer itself remains
unimportant until it is used by a person hammering and becomes present at hand (or
ready to hand). For the Speculative Realists, this leaves a large area of potential
analysis undeveloped and “condemn[s] philosophy to operate only as a reflexive meta-
critique of the conditions of knowledge.”45 To avoid this trap, Speculative Realists
claim that reality has to be independent of human subjectivity in order to be called
reality and, therefore, must be inherently nonhuman and “weird.”46 A human-
independent reality also results in the potential for analysis of the elements of that
reality: what have traditionally been called objects. Bogost calls for Speculative
Realism to examine the relations between objects outside of their involvement with
humans. He gives the example of an udon noodle:
For the udon noodle, the being of the soup bowl does not intersect with
the commercial transaction through which the noodle house sells it, or
the social conventions according to which the eater slurps it. Yet there
is no reason to believe that the entanglement in which the noodle finds
itself is any less complex than the human who shapes, boils, vends,
consumers, or digests it.47
Here Bogost tries to break apart the human elements that the noodle would normally
be wrapped up in (commerce, social conventions of eating) and creates a call to focus
on how the noodle becomes entangled with the other objects around it. These objects
could include the other ingredients in the soup, the bowl itself, the microbes and
particles in the air, or the spoon that dips down into the bowl periodically. For
Bogost, such an examination would give an idea of what the being of the udon noodle
is and expand philosophical investigation beyond just the conditions behind which
human knowledge is created.

49
Bogost makes the claim that Speculative Realism, and specifically his sub-
field called Object Oriented Ontology, succeeds where posthuman discourses have
failed. He says that “posthuman approaches still preserve humanity as a primary actor.
Either our future survival motivates environmental concern, or natural creatures like
kudzu and grizzly bears are meant to be elevated up to the same status as humanity.”48
Moving beyond anthropocentric discourse for Bogost and other Speculative Realists
means not centering discussion on how objects exist for humans or how they change
human consciousness, such as in Heidegger’s example of the hammer. This is not to
say, however, that human consciousness or human concerns do not figure into Object
Oriented Ontology or Speculative Realism. Human consciousness is a factor in these
examinations, but not the central point. As Bogost himself points out, understanding
the intentionality of a particular technology from its own point of view (an “objective
phenomenology” or the “weird,” nonhuman reality) is impossible for human
consciousness simply because human being is not the same as the being of a
technological artifact.49 We do not know what it is like to be an x-ray because we are
not x-rays. We do not know the inner workings of an udon noodle’s being because we
are not udon noodles. The closest we can come to understanding this “weird
phenomenology” is through analogy and metaphor, by putting it into a form that can
be processed by human consciousness. We can perform a phenomenology of an udon
noodle by placing it within a context of objects that are engaged with human
intentionality, such as the bowl, the soup, and the spoon. Analyzing the intentionality
of a car, for example, would also not result in an objective presentation of exactly

50
what it means to be a car. Instead, it would involve looking at the possibilities that
emerge from cars: new understanding of distance and time, potential for crashing,
different social status from owning a particular car, etc. We can only create an
ontology of the car that says that it intends in a way that sees the world like a system
of objects that each require calories, like an engine that requires fuel. Object Oriented
Ontology and Speculative Realism attempt to take materiality and the effects of
objects on situations and power relations into account.
Due to the radical de-privileging of the human with Object Oriented Ontology
and Speculative Realism, it would seem that it also does away with the potential for
developing the feminist aims of other strands of critical posthumanism. By removing
subjectivity from a privileged place and concentrating on the ontology of objects,
there appears to be no room for a politics of identity or developing a method of
working against oppressive gendered and racial power structures. Or, to an even worse
end, the hidden white, male objective viewpoint of humanism would be reinscribed
within critique, undoing the work of earlier feminist posthumanists.
The navigation of this divide is difficult even from within Object Oriented
Ontology and Speculative Realism, where the scholars developing the field are very
aware of the feminist origins of their emerging field.* The focus on objects does
*
A recurring track at the Society for Literature, Science, and the Arts conference in recent years has
been organized around Object Oriented Feminism and investigated what OOO Feminism would look
like. Hayles, Bogost, Morton, and others have all presented at this panel at various times.
Responding to the 2010 panel, Bogost pointed out that the discussion didn’t really provide a definition
of OOOF, but that doing so would have been counter to the spirit of OOOF and resulted in a
“domestication” of the area of study (http://bogost.com/writing/blog/object-oriented_feminism_1/).
Instead, the panel ended up arguing for a flexible line of critique that “making insides and outsides

51
downplay subjectivity and identity as the central focal point of critique, but as Levi
Bryant argues, this does not mean that investigations into power relations disappear.50
To the contrary, the major goal of Object Oriented Ontology is to trace power
relations over a broader spectrum that includes and starts from objects. By beginning
with objects, Object Orient Ontology seeks to explain what sort of material forces are
involved in the creation of categories of gender, race, class, etc.51
As with the critical posthumanism of Hayles and Haraway, I would argue that
Object Oriented Ontology does not completely eradicate the human, but provides an
opportunity to move beyond the humanist tendency to provide a single, universal
model for what should be human. Where Hayles and Haraway point to a multiplicity
of identity that disrupts overarching concepts of gender, Object Oriented Ontology
allows us to explore the situatedness of the human and begin an examination of the
milieu of intentionalities, technologies, and power relations that influence identity
and subjectivity. From this methodology and critique it is useful to re-examine the
domain intimately connected with the formation of the human within humanism:
medicine.
The current state of medical practice provides a fruitful landscape to perform
this task. While Lasik surgery and cochlear implants represent a use of technology that
promote a certain ideal of how a human body should function, other groups take these
same technologies and use them for ends that can not be universalized into a common,
shared notion of the human. Notably, these groups include individuals who engage
accessible and welcoming, whether they involve rights, ideals, identities, or everyday practices.” The
following chapters of the dissertation are, in many ways, an investigation of what making “insides and

52
with self-tracking practices. This can include diabetics who adapt doctor’s orders to
their own lives as they organize regimes of insulin injections, food consumption, and
exercise in unique ways. It can also include members of the Quantified Self
movement, who track various aspects of their lives in order to find out information
about themselves and to assemble large amounts of health data that can bolster data
collected by medical institutions. Much like Object Oriented Ontologists, these self
trackers begin with no assumptions about identity and use technology to provide
different perspectives on how they should organize their practices of self-care. From
the results of these tracking practices, as will be shown in Chapter 2 and 3, these
individuals organize ad hoc identities that are constantly in flux and constantly being
critiqued. They do not fit a normate model of what it means to be human, but limit the
scope of their construction of the human to a single individual. At the same time,
however, these identities will be shown in Chapter 4 to be engaged in an ethical
engagement with one another in a way that does not rely on a shared concept of the
human, but a mutual respect for multiple possibilities of being human.
1
Popper, Ben. The Verge. August, 2012. Print. <http://www.theverge.com/2012/8/8/3177438/cyborg-
america-biohackers-grinders-body-hackers>.
2
Halliwell, Martin, and Andy Mousley. Critical Humanisms : Humanist. Edinburgh: Edinburgh
University Press, 2003. 16.; Hayles, N Katherine. How We Became Posthuman: Virtual Bodies in
Cybernetics, Literature, and Informatics. N.p.: University of Chicago Press, 1999.; Derrida, Jacques.
"The Ends of Man." Philosophy and Phenomenological Research 30.1 (September, 1969): 31-57. Print.
3
Badmington, Neil. Posthumanism. N.p.: Palgrave Macmillan, 2000. 3.
4
Descartes, René. Key Philosophical Writings. Hertfordshire: Wordsworth Editions Limited, 1997. 108.
5
Descartes 109
6
Descartes 107
7
Descartes 107
outsides accessible” would look like as individuals use health tracking technologies to disrupt various
stable subject positions, institutional models of the human, and identities.
53
8
Descartes 107
9
Castree, Noel, Catherine Nash, Neil Badmington, Bruce Braun, Jonathon Murdoch, and Sarah
Whatmore. "Mapping Posthumanism: An Exchange." Environment and Planning A 36.8 (2004): 1345
10
Foucault, Michel. "What Is Enlightenment." Ethics, Subjectivity and Truth. Ed. Paul Rabinow. Trans.
Robert Hurley. New York: The New Press, 1994. 313-315.
11
Horkheimer, Max, Theodor W Adorno, and Gunzelin Schmid Noerr. Dialectic of Enlightenment :
Philosophical Fragments. Stanford, Calif.: Stanford University Press, 2002. Also Kant, Immanuel.
"What Is Enlightenment." www.columbia.edu. Web. 13 May 2016.
<http://www.columbia.edu/acis/ets/CCREAD/etscc/kant.html>.
12
Kant
13
Kant
14
Roden, David. Posthuman Life: Philosophy at the Edge of the Human. N.p.: Routledge, 2014. Google
Scholar. Web. n.d.
15
Roden
16
Roden
17
Roden
18
Davies, Tony. Humanism. London ; New York: Routledge, 2008.
19
Foucault, Michel. The History of Sexuality. N.p.: New York, Pantheon Books, 1978. 38
20
For a full account of the murder and trial, see Forbes, John. The Cyclopaedia of Practical Medicine.
Vol. 4. N.p.: Blanchard and Lea, 1854. 52-53.
21
Foucault, Michel. "Abnormal: Lectures at the Collège De France, 1974-1975, Edited by Valerio
Marchetti & Antonella Salomoni, Translated by Graham Burchell." New York: Picador (2003). 117,
22
Foucault “Abnormal” 130
23
Foucault “Abnormal” 131
24
Foucault, Michel. The Order of Things : An Archaeology of the Human Sciences. New York: Vintage
Books, 1994. 387.
25 Roden
26 Roden
27 Roden
28
Moravec, Hans. Mind Children. N.p.: Cambridge Univ Press, 1988.
29 Roden
30
Halliwell, Martin, and Andy Mousley. Critical Humanisms : Humanist. Edinburgh: Edinburgh
University Press, 2003. 25.
31
Haraway, Donna. Simians, Cyborgs, and Women. New York: Routledge, 1991. 188.
32
Haraway, Simians, Cyborgs, and Women. 188
33
Haraway, Simians, Cyborgs, and Women. 151
34
Hayles, N Katherine. How We Became Posthuman: Virtual Bodies in Cybernetics, Literature, and
Informatics. N.p.: University of Chicago Press, 1999. 2-3.
35 Roden
36
Miah, Andy. "Posthumanism: A Critical History." Medical Enhancements & Posthumanity. New
York: Routledge, 2007. 7-8.
37 Roden
38 Hayles 2-3
39 See Hayles and Derrida
40 Hayles 286-87
41 Halliwell 15
42 Roden
43
Heidegger, Martin, Joan Stambaugh, and Dennis J Schmidt. Being and Time. N.p.: SUNY Press,
2010.
44
Bogost, Ian. Alien Phenomenology, or What It's Like to Be a Thing. N.p.: U of Minnesota Press, 2012.
5
45
Harman, Graham. "Guerilla Metaphysics." Phenomenology and the carpentry of Things. Chicago:
Open Court (2005). 42.
46 Roden
47 Bogost 30
54
48
Bogost 7. Also note that this is one of Bogost’s main criticism of the strikingly similar actor-network
theory. Bogost claims that in Latour’s theory, “analysis still serves the interest of human politics”
49
Bogost 64. Again, Bogost is working primarily from OOO, a similar yet slightly different system of
thought than postphenomenology.
50
Bryant, Levi. "Worries About OOO and Politics." Larval Subjects . larvalsubjects.wordpress.com.
Web. 13 May 2016. <https://larvalsubjects.wordpress.com/2012/05/29/worries-about-ooo-and-
politics/>.
OOO and SR are fairly new and developed by scholars heavily involved with contemporary
technology, so much of the discussion and clarification happens through blogs, Twitter, and other social
media platforms.
51
Trombley, Jeremy. "Ethics and Politics: What Are You Asking?" Larval Subjects .
larvalsubjects.wordpress.com. Web. 13 May 2016.
<https://larvalsubjects.wordpress.com/2012/05/29/ethics-and-politics-what-are-you-asking/#comment-
133863>. As noted above, much of the development of OOO and SR occur on blogs and online forums.
This particular comment was referenced by Bogost when explaining the politics of OOO and SR.

CHAPTER 2
Diabetes Self-care Techniques
The previous chapter identified principles of exclusion as a major issue that
arises from the proliferation of humanism, even as humanism has claimed to uphold
Enlightenment values of justice, ethics, and critique that should result in a more
democratic and inclusive society. Various posthuman critical theories have identified
the figure of the normate human as a dangerous construct that limits political, social,
and economical engagement for groups that are non-Western and non-white (post-
colonialism), non-male (feminist and gender studies), or unhealthy (disability studies).
While the logic of humanism works through a variety of different areas and
institutions, medical practice is one of the most significant because, as Michel
Foucault points out, it not only lays claim to what a “healthy” individual is, it also
dictates how a person should attempt to fit into society at large.1 One such example
began in the 1960s, when the Women’s Health Movement pointed out that the current
medical and legislative systems did not account for the bodies of women.2 The
Women’s Health Movement’s original target was reproductive rights, but this quickly
expanded to incorporate the lack of women as the object of clinical studies,
participants in clinical trials, and senior investigators involved with the trials.3 By
positioning women as a different type of body that needed a different type of medical
care, the Women’s Health Movement recognized the inability of a universal, normate
model of the human to accurately cover all people and identified that universal model
of the subject to be heavily gendered as male.
55

56
Beyond the Women’s Health Movement and other liberation movements of the
1960s, the postmodern turn in the late twentieth century resulted in critiques of “the
human” in areas such as gender studies, post-structuralism, post-colonialism, post-
Marxism, and postmodernism at large.* While each field had a different goal, many of
them rested on the idea that the subject created by the idea of Man reflected a rational
Western male sensibility and excluded a particular type of individual, resulting in an
imbalance of power. For gender studies, the excluded subject was the non-
heterosexual male subject, including female, LGBT, and queer subjects. For post-
structuralism, the normative subject in general was called into question, as the
legitimacy of the characteristics making up the “typical” human was shown to be
baseless.† Post-colonialism identified the non-Western subject as the excluded
individual. Post-Marxism looked at the ways in which hegemony and class identity
*
Note that many of these fields owe a debt to Foucault’s writings, but that is not to say that each came
about as a direct result of Foucault’s thought. Rather, they are brought up to point to a shift in thought
in the late twentieth century that called into question the existence of a “normal” human.
Unpacking the entirety of each of these disciplines’ relation to a critique of a “normal” subject would
warrant a much larger investigation than is within the scope of this paper. However, for some
information on each, see:
Gender Studies: Julia Kristeva, The Kristeva Reader; Gayatri Spivak, “Can the Subaltern Speak”; Judith
Butler Gender Trouble and Bodies That Matter; and Luce Irigaray, The Sex Which is Not One
Post-structuralism: Jacques Derrida, Of Grammatology and "Structure, Sign, and Play in the Discourse
of the Human Sciences”; and Roland Barthes, S/Z.
Post-colonialism: Edward Said, Orientalism and Franz Fanon, The Wretched of the Earth.
post- and neo-Marxism: Jean Baudrillard, Simulacra and Simulation; Frederic Jameson,
“Postmodernism, or the Cultural Logic of Late-Capitalism”; and Theodor Adorno and Max
Horkheimer, The Dialectic of The Enlightenment.
Note that this is far from an exhaustive list in each category.
†
It is worth noting here that Foucault often falls into the post-structuralist category.

57
benefit particular subjects at the cost of others. Many of these areas of study overlap
with the others and is seldom mutually exclusive.*
Along with the critique about who can be “human,” posthumanism began to
question what could be human. The posthuman emphasis on embodiment, dispersal of
consciousness, decreased focus on rationality as a defining characteristic of the
human, and the body’s ability to integrate with technology makes an attempt at
creating a non-anthropocentric subject.† Medical technologies like glucose monitors,
accelerometers, and activity tracking software all play a large part in posthumanist
discourse, as they are prime examples of how technology can be used to privilege
information about the body and de-center focus on consciousness. As chapter one
shows, however, these technologies provide information on a human body, putting
them in line with the observation of Hayles, Derrida, and others that posthumanism
actually retains some type of subject that could be called “the human.”
Posthumanist technologies may retain some idea of “the human,” but it
drastically reconfigures that notion in ways that allow it to be constructed along much
more unique, flexible lines. Such a construction is prevalent in chronic illness, where
self-care techniques are employed not to enable full recovery from a disease, but as a
necessity to continue normate biological life by suppressing symptoms and delaying
fatal complications. Diabetes provides a strong example of these types of self care
*
Also note that often, many of the scholars within these categories disagree with each other or have
varying degrees to which they move away from the idea of a naturalized concept of the human.
†
This definition comes from Hayles, N Katherine. How We Became Posthuman: Virtual Bodies in
Cybernetics, Literature, and Informatics. N.p.: University of Chicago Press, 1999. See Chapter 1 for a
more complete exposition of posthumanism.

58
techniques, as it is considered an incurable disease that can be kept under control with
proper management and rules laid out by medical practice. With the rise of
contemporary technologies such as continuous blood glucose monitors and an
increased emphasis on patient self-care, diabetes care integrates the body with
technology in a way that is neither strictly managed in clinical settings, nor left
entirely up to the patient. Additionally, the discourse surrounding diabetes care views
the diabetic patient as an embodied individual that is defined just as much by the
characteristics of the disease as they are by their consciousness, as in posthumanism.
Thus diabetes becomes not an abstract disease that needs to be dealt with, but a set of
practiced object. Defining diabetes in terms of a “practiced object” takes it out of the
clinical setting and into the lives of the patients while emphasizes the techniques of
care the patients use. Though diabetics do visit the doctor for some treatment, they do
most of the work caring for their disease on their own. The life of the patient has to be
organized around the limitations and affordances of diabetes: certain food must be
avoided, exercise regimes must be followed, and medicine must be taken at certain
times. Diabetes, then, becomes more than just a “thing” that the patient has or doesn’t
have, but a whole new set of practices and relations in which the patient engages. By
becoming more than an object that can be studied in isolation from the body it
inhabits, diabetes disrupts the medical gaze to produce a unique subject that creates a
model of a “normal human” that only applies to itself even as it references clinical
medical knowledge.

59
Twentieth century medical discourse has found that diabetes affects how the
body processes its main source of energy: glucose.4 Non-diabetic bodies break down
food into glucose, or blood sugar, which then moves to the bloodstream in order to be
used by cells in the body.5 But in order for this process to occur, the hormone insulin
must be present in order to convert the glucose into a usable form. Diabetic bodies
have a pancreas (the organ that produces insulin) that does not create enough insulin
or contains beta cells that are unable to use the insulin that is produced. This means
that the glucose from food builds up in the bloodstream and comes out of the body
through the urine instead of being used for energy.
There are three main forms of diabetes: Type 1, Type 2, and gestational
diabetes.* Type 1 diabetes is a condition whereby the body destroys the insulin-
producing cells in the pancreas, a particular type of islet cell called beta cells. Without
*
The cross section of at-risk individuals for diabetes is particularly interesting. Much of the literature
divides it among one of two lines: race and weight. Gender is addressed, but instances of diabetes are
roughly equal between men and women. The exact cause of Type 1 diabetes is unknown, but it does
appear more often in whites than it does in non-white individuals. Type 2 diabetes occurs often in
“African Americans, American Indians, some Asian Americans, Native Hawaiians and other Pacific
Islander Americans, and Hispanics/Latinos” according to the National Diabetes Information
Clearinghouse. Additionally, Type 2 diabetes is typically associated with obese and overweight
individuals, linking the disease to unhealthy eating habits.
There is a good deal of work that could be done to analyze diabetes in terms of producing an idea of
essential qualities belonging to particular races or the link to particular socio-economic statuses.
Additionally, looking at diabetes in terms of the “War on Fat” and increase in health consciousness
could prove interesting discussions.
However, this chapter is primarily concerned with the role that diabetes management plays in
constructing a body with a particular relation to the posthuman. I am more interested in how the
diabetic individual situates themselves within a nexus of other subjects, objects, technologies, and
medical discourses than I am looking at the place of diabetes within culture, though that aspect of
diabetes could provide insights into particular power structures and hierarchies.

60
a way to produce insulin, the Type 1 diabetic has to take insulin daily in order to avoid
diabetic ketoacidosis, or a potentially fatal diabetic coma.6 Type 2 diabetes, unlike
Type 1, is linked to certain conditions of life, including older age, obesity, family
history of diabetes, previous history of gestational diabetes, physical inactivity, and
certain ethnicities.7 In this type of diabetes, the body cannot process the insulin that it
does produce and creates a resistance to that insulin. Over time, the body lowers its
production of insulin, which in turn disrupts the body’s ability to turn glucose into
energy and leads to kidney disease, nerve damage, eye problems, and stomach
problems.8 Gestational diabetes is considered one of the three main types, but is
temporary – not chronic like Type 1 and Type 2 – and only occurs during pregnancy.
The cause of gestational diabetes is unknown. There are other types of diabetes, but
they are much less common. This paper will focus more on Type 1 and, to a lesser
extent, Type 2 diabetes because they are both chronic conditions that better exemplify
the need to order life within the context of the disease over the long term. Other forms
of diabetes may also demonstrate some of the issues discussed, but they do so in a
more subtle or partial way.
Typical symptoms of diabetes include an increase in thirst and urination,
hunger, weight loss, blurred vision, fatigue, and slow healing sores.9 These symptoms
can occur suddenly in Type 1 diabetics, but some Type 2 diabetics can go years
without seeing direct symptoms. They can also be mild or severe depending on the
See "Diabetes A-Z." National Institute of Diabetes and Digestive and Kidney Diseases. Web.
<http://diabetes.niddk.nih.gov/dm/pubs/overview/index.aspx#who> for an example of how diabetic
individuals are grouped.

61
situation. Many of these symptoms appear during “hypoglycemic attacks,” when the
body needs more glucose, when too much insulin is present (i.e. through insulin
injections), or when alcohol has been consumed.10 Hypoglycemic attacks can be
treated by adding more glucose to the blood stream, sometimes by the diabetic
individual themselves but in serious cases medical personnel have to attend to the
individual.
Type 1 and Type 2 diabetes are both chronic conditions that do not have a
definitive “cure,” but must be constantly managed in order to avoid the body shutting
down. A new pancreas can not simply be transplanted into the individual and no
medicine will remedy diabetes permanently. The disease must be lived with in
perpetuity and the focus of contemporary medicine has been on managing the
symptoms while also trying to avoid the emergence of major attacks on the body, such
as ketoacidosis (a diabetic coma). The diabetic individual must constantly manage
their disease and engage in the basic therapies of “healthy eating, physical activity,
and taking insulin (in the case of Type 1 diabetics) or monitoring blood glucose (in
the case of Type 2 diabetics).”11
The current institutional medical knowledge has changed drastically since the
first mention of diabetes in 1500BCE in Egypt and India. During this period, the
disease was characterized not by the body’s inability to produce insulin, but according
to the excessive urination it caused in those afflicted with it and its excessively sweet
character.12 From its initial identification, diabetes has been connected with various
technologies and self-care techniques. One of the first techniques of diagnosing

62
diabetes was to observe the attraction of ants and flies to the urine of a diabetic.13
Originally, medical knowledge had a very different model from contemporary
medicine and focused on attempting to locate and eliminate the cause of diabetes.* The
Greek physician Aretaeus of Cappadocia first hypothesized that the disease originated
in the bladder and kidney, but then attributed it to the bite of the mythical Dipsas
serpent.14 In the 17th century, Thomas Willis shifted the focus of medical knowledge
of diabetes from the causes to the symptoms. He noted that patients urinate frequently
and that the cause remained unknown. Even with hidden origins, he believed that the
disease could be cured by “restoring balance between the body’s various humors” – a
claim that would not hold up against current standards of medical knowledge creation
and legitimation.15 For Willis, the primary goal was functional: to remove the signs of
the disease and return the patient to a healthy state. Each case was unique and called
for its own curing method. Restoring the balance in humors for one person may
require a slightly different process than in another person. Overlooking the cause of
the disease in favor of alleviating the symptom of urination continued up until the
eighteenth century, when the clinic became the foundation of medical practice.
With the introduction of the clinic, medical knowledge began to shift from
taking the individual patient’s affliction as a unique case toward understanding disease
as part of a larger system. Foucault observes that the eighteenth century saw medical
*
Locating the cause of disease did not entirely disappear in later versions of medicine, but the way it
was enacted changed. At various points in time, other targets of research included trying to eliminate
symptoms, trying to harmonize the balance of humors in the body, locating the afflicted organ,
examining the disease on a molecular level, etc. before the current iteration that, according to Foucault,
63
knowledge as the creation of a “‘map’ (repérage): a symptom was situated within a
disease, a disease within a specific ensemble, and this ensemble in a general plan of
the pathological world.” Here, symptoms were more than just an affliction in a single
patient that could be cured, restoring the patient to health. Instead, the symptoms
indicated the presence of a disease that had its own properties and could manifest
itself in any person. And, more importantly, could be studied as an object in and of
itself.
Disease became more than a directly observable symptom that must be treated, as with
Thomas Willis’ focus on diabetes treatment in the 17th century. Instead, as David
Armstrong points out:
the symptom, as of old, was a marker of illness as experienced by the
patient, but to this indicator was added the sign – an intimation of
disease as elicited by the attentive physician through the clinical
examination. For example, the patient's symptom of abdominal pain
might be linked to the sign of abdominal tenderness that the physician
could discover; but neither symptom nor sign in itself constituted
illness: both pointed to an underlying lesion that was the disease16
As Armstrong claims, the symptom was no longer the endpoint of treatment in the 17th
century. It became a marker of a larger process taking place that spanned not only the
individual body of the patient but an affliction that could affect any human body. Such
a shift in thought began the process of thinking of the disease as an object separate
from its manifestation in the human body. This understanding of how symptom, sign,
and disease interacted became codified medical knowledge that expanded into a larger
way of thinking that directed the actions of patient and doctor, as well as entire
populations. The process of linking a sign to its corresponding disease did not occur
views disease as an entity that exists outside the body and can be studied independently of its individual

64
on the direct patient-doctor level, but rather by the doctor’s ability to apply a larger
body of knowledge to the specific case. As Foucault writes, the support of this new
medical system “was not the perception of the patient in his singularity, but a
collective consciousness, with all the information that intersects in it, growing in a
complex, ever proliferating way until it finally achieves the dimensions of a history, a
geography, a state.” Moreover, in “the clinic…one is dealing with diseases that
happen to be afflicting this or that patient: what is present is the disease itself, in the
body that is appropriate to it, which is not that of the patient, but that of its truth.”17 As
eighteenth century doctors encountered disease within the clinical setting, the disease
as an abstract object that could stand on its own eclipsed the idea of a patient with
symptoms that needed to be treated. By examining this disease, doctors could figure
out how it worked and, potentially, create a cure for all cases of the disease.
As knowledge of disease emerged as a geography of information that extended
beyond the body of the singular patient, that knowledge also began to encompass
entire populations that could be managed so as to express a medically-defined
normative set of health standards. Diseases became an object that were contagious and
could be passed among bodies in populations, not just isolated cases. To contain
diseases, the work of the doctor was not just to heal the sick, but to help coordinate
society through organizing knowledge in a manner that gave them administrative
power over the “conditions of life, housing, and habits, which serves as the basic core
for the ‘social economy’ and sociology of the eighteenth century.”18 Individuals were
manifestations in patients.

65
directed to follow public health’s proscription for a particular way of life that would
allow them to approximate “normal” and “healthy.” Foucault termed this new reach in
medical knowledge and organization “medico-administrative knowledge” to
emphasize the way medicine informed a general technique of health that affected all
areas of life in the eighteenth century.19
As it expanded beyond the doctor-patient encounter, medico-administrative
knowledge revolved around creating the idea of a universal model of the disease and
its manifestation. The main issue was not the unique case of the disease, but its
relation to a generalized system of disease that could apply to multiple cases. This
resulted in a shift of focus from curing or understanding the individual patient in its
unique manifestation of the disease into the creation of an abstract body of knowledge
on disease that could be continually added to and modified.
Matthew Davis, who is himself diabetic, identifies this shift away from the
patient toward the construction of a body of medical knowledge in the writing of two
authors on diabetes: John Rollo and Valentine Mott.20 Both authors write at the turn of
the 19th century and seek to add to a body of medical knowledge about the disease,
where the patient is not a unique case but an instance of the larger, abstract disease. To
do this, Rollo and Mott both follow the process unique to 19th century medicine that
Foucault identifies as “the medicine of sick organs.” In this type of medicine, the sick
organ is identified, then the doctor explains how that organ became sick, and then
finally indicates how the illness could be stopped. In his work The History, Nature
and Treatment of Diabetes Mellitus, Rollo identified and verified the existence of
diabetes

66
through blood tests after recognizing the already known symptoms of “weight loss,
keenness of appetite, clear urine, wasting of flesh" and recording several new
symptoms as well.21 He then identifies the stomach as the primary organ of concern
and makes an attempt at countering “the disastrous effects of ‘luxurious living’” by
“reversing the production of urine and reducing the amount of sugar in the blood
stream by altering the quantity and quality of food ingested.”22 Specifically, Rollo
suggested avoiding vegetables and consuming mostly meat. As with the typically 18th
century “medicine of sick organs,” Rollo here identifies the stomach as the organ
causing diabetes, claims that the organ became sick through too much luxurious food,
and recommends that the process be reversed by proper eating. Mott’s process builds
on Rollo’s, first identifying the disease in the same manner as Rollo and asserting that
it comes from a sick stomach. However, he is unable to cure the disease according to
Rollo’s method of dietary modifications, so he advocates bleeding the patient. When
this failed, he turns to administering laudanum, opium, and arsenic, which also do not
cure the disease.23
Rollo and Mott’s lack of success is less important than the methods they
utilized in engaging with the disease. The process that they followed was repeated by
other 19th century physicians and created a body of medical knowledge that relied on
observation and speculation. The sick patient was no longer the sole subject of these
medical investigations, but was interpellate into a set of practices whose aim was to
create a “coherent ‘theory’ of diabetes treatment” that was universally applicable. As
with other investigations into medical afflictions, this “coherent theory” of diabetes

67
treatment became not just a method of restoring the patient to health through the
application of universal principles, but a method of governing the patient’s life by
formulating a system of how the patient should care for himself. In the case of 19th
century diabetes treatment, these life-governing recommendations came through
repeating Rollo’s meat-centric “animal diet” and adding the suggestion that patients
engage in physical activity.24 Doctors such as the prominent Charles H. Pile and
Charles B. Brigham claimed that even though these measures would not cure diabetes,
they would help the patient live a longer life.
Importantly, production of knowledge about diabetes in the 18th and 19th
century took place in the clinic through studying patients and their afflictions.
Previously, patient care had taken place within the homes of patients, a practice
medical historians term “Bedside Medicine”.25 Within Bedside Medicine, the natural
place of disease was located in the home, among the patient’s typical surroundings and
family. It was in that location that the individual case of the disease could be identified
and cured. However, the shift to clinical medicine (also called “Hospital Medicine” by
some medical historians) and the growing desire to de-individualize care in favor of
building a body of medical knowledge also moved the site of patient care to the clinic.
The clinic existed as a neutral space, untouched by the individual characteristics of the
home, in which the disease could be isolated and identified “without the contaminants
of extra ‘noise’” – i.e. germs. By creating a neutral space, the clinic further extracted
the individual from their diseased body, making the patient an instance of the disease
that could be studied and broken apart in service of a corpus of medical knowledge.

68
Frederick Banting and Charles Best are largely credited with being the first to
develop insulin as a treatment for diabetes and, in the process, dramatically changing
the way that diabetes care was enacted. Banting and Best performed experiments in
the early 1920s removing the pancreas of a dog and observing the resulting diabetes.
By then grinding up the pancreas and injecting it back into the dog, Banting and Best
were able to alleviate the dog’s symptoms of diabetes. The extract that resulted from
grinding up the pancreas was named “insulin.” By 1923, Eli Lilly was mass producing
insulin as a treatment for diabetes. In the following decades, research on insulin
continued, resulting in increased availability and a synthetic version.26
Banting and Best’s experiments coincided with a shift in how medical
knowledge was created at the beginning of the twentieth century. The clinical
knowledge of the eighteenth and nineteenth centuries was amplified through the rise
of the laboratory. N. D. Jewson has pointed out that in Laboratory Medicine, “the
patient was removed from the medical investigator’s field of saliency altogether."27
Labs conducted research on diseases without the patient present, instead focusing on
the “fundamental particles of organic matter.”28 Diabetes care was no different. Where
Rollo and Mott examined single patients to draw out facts about diabetes and then
recommended cures to those specific individuals (even as the cures were based on
abstract knowledge of the disease), Banting and Best looked at the function of the
pancreas and the chemicals within it. Their first subject was neither human nor
diabetic, as with Rollo and Mott. The dog that they examined did not have the disease
until they removed its organ, and only then did they have a patient that was a diabetic

69
subject.* It was only after they had significant successful results from injecting the dog
with “insulin*” that Banting and Best tried the treatment on humans. The development
of refined and synthetic insulin in the following decades also occurred within the
laboratory, away from physical patients. As with clinical medicine, these experiments
were performed with an eye toward adding to the archive of medical knowledge
surrounding diabetes. In turn, this knowledge could be used to proscribe “healthy”
ways of living for populations that would, theoretically, result in the disappearance of
the disease. In a radical extension of the configuration found in clinical medicine
where “doctors and patients…are tolerated as disturbances that can hardly be
avoided”, laboratory experiments surrounding diabetes in the 20th century removed
contact with the doctor and patient entirely.29 The individual appeared here only as an
abnormal, unhealthy subject that must be treated because they did not follow the
medico-administrative guidelines set out by laboratory medicine.
As the research aspect of clinical/laboratory medicine’s investigations into
diabetes moved further toward a dissolution of the unique patient in the service of
creating a totalizing body of knowledge on the disease, it failed to find a cure for the
disease. The discovery of insulin was a success for prolonging the life of diabetes
patients and finding the processes at work behind the disease. But, it was unable to
fully restore the diabetic patient to a consistently healthy state and moved the focus of
*
An investigation into the significance of the shift to animals rather than human patients could also be
carried out here. Though this project is concerned with the role of the human within discourse, I am
more concerned with how human subjectivity is formed within processes of self care rather than how it
plays out directly within the laboratory setting.

70
the medical discourse to the methods of treatment and disease management. As Davis
points out:
Diabetes did not develop from an incurable, fatal disease into a curable
ailment. Instead, insulin is an ongoing form of treatment. The
symptoms, methods of diagnosis, or causes of diabetes are no longer
important places for an investigation of the cultural construction of the
diabetic body. Instead, the focus radically shifts toward treatment, i.e.
the manner in which the diabetic patient negotiates the medical
discourse in order to regain control of bodily ebbs and flows.30
Davis’ remark points to the unique character of diabetes (and many chronic illnesses)
whereby the clinical/laboratory model of medicine cannot completely dissociate itself
from the patient. The disease cannot be dealt with only in the sterile and neutral space
of the clinic or laboratory, but must rather take into account the patient’s negotiation
“of the medical discourse in order to regain control of bodily ebbs and flows.” As
diabetes research moved increasingly toward abstraction and creating knowledge of
the disease on the molecular level, the actual processes of diabetes care moved in the
opposite direction, engaging the patient in a complex system of acceptance,
cooperation, and resistance that required treatment to take into account the
individual’s everyday, embodied experience. The discovery of insulin as a treatment
for diabetes allowed the patient to manage their diabetes from the home, rather than
the clinic, under the direct supervision of a doctor. In order to deal with their
symptoms, patients could now administer insulin of their own accord. They became
“physicians unto themselves.”31 While the patient takes on this burden, they are either
ordering their techniques of care according to the directions of doctors and medical
*
As noted above, this was actually the dog’s ground up pancreas, not refined insulin. I use the term

71
knowledge or modifying that system, whether intentionally or unintentionally. In the
late 20th century and early 21st century, this process involves the patient examining
their own blood sugar levels through a glucose monitor and then injecting a particular
amount of insulin depending on their sugar levels. The patient has a certain dosage of
insulin recommended by their doctor and informed by the medico-administrative body
of knowledge surrounding diabetes, but it is ultimately up to the patient to marshal the
care and monitor their actions. Such a relation between knowledge and day-to-day
care creates new spaces for control that extend into the life of the patient, but also
open up sites of resistance.
The “treatment” for diabetes is, in many ways, unique because it focuses not so
much on the administration of particular medicines, but on the ordering of a particular
form of life that occurs at the intersection of medical practice and the patient’s own
agency in following medical prescriptions. Rather than a straightforward instance of
the medical gaze disciplining the patient, the actions of the patient drift among willing
submission to the medical gaze, a conscious refusal to follow the treatments provided
by clinical medicine, and attempting to respond to unexpected actions of the body that
have no identifiable cause. Illnesses such as asthma, bipolar mood disorder, Crohn’s
disease, epilepsy, and other chronic conditions all require the continuous
administration of medication while diabetes discourse also privileges eating properly
and being somewhat active, even in the case of Type 1 where the effectiveness of
“insulin” here for simplicity.

72
these techniques are not as drastic as with Type 2 diabetes.* Moreover, the patient has
significant control over their dosage of insulin rather than administering an amount
pre-measured by a doctor, moving a large portion of the responsibility of care to the
patient themself.† Such a move provides a situation whereby clinical medicine is
responsible for the overall well-being of the patient, yet the patient must direct their
own day-to-day care. In effect, clinical medicine provides guidance based on claims
for the patient’s well-being, rather than discipline over the patient’s actions.
Disciplinary actions, formerly a product of the medical gaze, become self-imposed on
the patient as they willingly manage their disease informed by the suggestions of
clinical medicine in order to lessen symptoms and have a functional body. The issue,
however, is when clinical medicine cannot account for the individual embodied
situation of the patient, requiring the patient to override or supplement medical
knowledge with their own methods of managing care. By examining the cases of Type
1 diabetics, it will be possible to see how patients engage in techniques of self care
based on medical recommendations in order to manage their disease, but also go
beyond those recommendations to fit their unique circumstances by utilizing various
tracking technologies. These digressions are seen by medicine as a noncompliant
patient, yet such noncompliance proves necessary to manage the disease in everyday
life.
*
See below for a more in-depth discussion of this issue, but some Type 1 diabetics are recommended
strict control even though research has shown that strict control is only significantly effective with Type
2 diabetes.
†
This is not to say that some of the points that I make about diabetes management could not pertain to
other chronic illnesses, only that diabetes presents an extreme case that makes these points come out

73
Scholar Matthew Davis recounts his own experience with diabetes as a way to
demonstrate clinical medicine’s apparent increase in the regulation of daily life for an
ideal patient – an account that seems to go along with Foucault’s notion that medicine
attempts to create a model of the “healthy” human. Though Davis himself believes
that his experience maps onto the model of the medical gaze, it is possible to see
small breaks in his process of self-care and treatment, which point to the patient as not
just willingly engaged in reproducing the medical gaze, but also a necessary force in
changing medical recommendations to fit an individual situation. Davis observes that
when he was first diagnosed with Type 1 Diabetes, the treatment protocols were much
more lax. But in recent years, management of his disease has come under closer
scrutiny by his doctors even though he is largely responsible for enacting the
recommendations outside of the clinic. This shift, for Davis, represents the ever-
expanding control of the medical gaze into the daily life of the compliant patient. He
writes:
[Initially, i]nsulin was used to lower blood sugar levels, but tight
control was not encouraged, and many common diabetic complications
were considered unavoidable. Although glucose levels for a non-
diabetic individual vary between 80 and 120 milligrams of glucose per
deciliter of blood (mg/dL), my doctor advised me to maintain blood
glucose levels below 200 mg/dL, and to not bother adjusting my
insulin levels if these goals were met. As this advice demonstrates,
‘adequate training is still not obligatory. Instead, simply handing the
patients insulin, syringes and a book telling them to get on with it and
become streetwise by a process of trial and error is still considered an
option' (Berger and Mühlhauser, 1993, p. 322). My diabetes controlled
in this manner, visits to the doctor became necessary only once a
year.32
more clearly. Any chronic illness requires a significant amount of the life of the patient (and, many
times, close friends and family) to be ordered.

74
When he was first diagnosed, Davis had a certain degree of freedom with his
program: there were infrequent visits with his doctor and he could decide when and
where to take his insulin. But, there was still some medial oversight. His doctor
recommended that he keep blood glucose levels below 200 mg/dL – an amount based
not on the makeup of Davis’ own body, but on the general and abstract
recommendations originating in clinical medical knowledge. Additionally, Davis’
entire treatment program of blood glucose monitoring and insulin injections was
handed down from clinical medical knowledge. He was instructed to keep these
glucose levels throughout the day as he performed his daily tasks, not only during his
doctor’s visits. Davis could make some choices about how to administer his treatment
while still remaining compliant according to the recommendations of the doctor.
Davis goes on to show how in recent years clinical medicine has attempted to
increase its control over the regulation of his treatment. These changes came in the
wake of the findings of the Diabetes Control and Complications Trial, a clinical trial
conducted from 1983 until 1993 that found that progression of diabetes-induced eye,
kidney, and nerve damage could be contained by keeping blood glucose levels as
close to normal as possible.33 The official recommendation of the American Diabetes
Association then became to encourage patients with any type of diabetes to have
extremely tight control over their glucose levels throughout the day. For David this
treatment, called “intensive therapy,” involved “new goals for blood sugar levels,
more frequent checking of blood glucose levels, and twice as many daily injections of
insulin” as well as “a week-long diabetes management course, and [an increase of]

75
visits to the doctor to four times per year, with additional appointments with dietitians,
nurses, podiatrists, and eye doctors.” He points out that even medical knowledge does
not deem this method of treatment effective for his own case of Type 1 diabetes,
though the ADA recommends all individuals with diabetes follow this plan. In Davis’
view, this shift in treatment was designed primarily to reaffirm “the doctor's role in
assisting the patient to achieve control over his or her errant body, thus minimizing
the patient's feelings of autonomy in guiding his or her own treatment." As with
Foucault’s clinical medicine, the treatment recommendations utilize discourses of
creating a healthy patient paired with treatment protocols to which the patient cannot
have direct access. According to Davis’s account, through submission to the medical
gaze and its ordering of daily life, the patient begins to act like a normate human as
conceived by clinical medical discourse.
Davis presents an account of expanding medical control throughout process of
self-care in diabetes management that is backed up by the suggestions of the medical
field itself. To increase the frequency of checking glucose levels for diabetic teens,
Anderson et al recommends increasing parent involvement.34 Borus and Laffel provide
a review of multiple studies and come to similar conclusions, advising not only
increase in parental involvement, but also increase in provider contact through text,
email, and follow-up visits.35 These recommendations are in line with Davis’ fear that
diabetes management has increased the oversight of the medical gaze into daily life.
These studies give justification for increased contact with care providers outside of the
bounds of the clinic while bringing in family members to act as watchful eyes that

76
encourage compliance. However, even these recommendations do not provide an
absolutely compliant patient. Individuals often do not put into practice the required
medical directives, for reasons ranging from lack of knowledge to conscious
unwillingness to unexpected bodily reactions to situations that do not allow self care
to be administered (such as being at an upscale dinner or napping).
The persistent lack of this perfect patient has become a focus of a great deal of
medical discourse in the twentieth century.36 As medicine expanded its knowledge
beyond its own domain into medico-administrative knowledge that spanned social
relations and ways of life, it also became concerned more with how well the patient
complies. In the early twentieth century, this involved adding nutritional supplements
to food and engaging with food producers to recommend a dietary regime that could
be packaged and sold.37 Here, doctors used market forces, food regulations, and other
systems of administrative knowledge to ensure patient compliance to clinical
recommendations. In the early-to-mid twentieth century, the development of
antibiotics – what Haynes and others call the first “truly effective” medicine –
allowed for doctors to become even more concerned with compliance and the
ordering of individual patients’ lives.38
Thousands of studies have been done to identify the causes of noncompliance
and potential ways to fix the problem.39 R. Brian Haynes, one of the major
commentators on compliance, summarizes these, stating that compliance with short-
term treatments can be helped through a combination of “clear instructions; recalling
non-attenders; patient self-monitoring of compliance and/or treatment outcomes;

77
enhancement of social support; ‘contingency contracting’ and rewards or
reinforcement for high compliance; and group discussion and supervised self-
management.“40 He also notes that long-term compliance aids must be constantly
administered by a doctor otherwise the patient will slip back into noncompliance.41
Other researchers such as Katie Buston present causes for noncompliance that
put the burden squarely on the patient. She lists forgetfulness, ineffective medication,
denial, difficulty using apparatuses, inconvenience, embarrassment, fear of side
effects, and laziness as major causes to noncompliance.42 Buston, as with other
researchers, advocates for more clinically-sanctioned information to be provided to
the patients or better communication on the part of the doctor to increase compliance.
Scholars like Haynes and Buston view the patient as an initially non-compliant subject
that must be disciplined through clinical oversight and engaging with medical
knowledge. It is medicine’s duty not necessarily to make the patient well or to bring
the patient into the process of producing medical knowledge, but to organize the
patient’s habits, treatment protocols, and everyday life in a way that fits with medical
best practices.
But even as some medical scholars have developed ways to try and increase
compliance in patients through interaction with doctors and medical knowledge, there
has been a push-back on the formulations of noncompliance from sociology,
anthropology, and even medicine itself. From the perspective of social scientists and
humanities scholars, compliance is a particularly troublesome issue because of the
technologies of control that it uses. Anthropologist James Trostle points out that even

78
under different names, “compliance” becomes an ideology that asserts control over the
patient by the doctor, allowing the doctor to perform a judgment and apply a label
rather than understand the point of view of the patient.43 In place of talk of
compliance, Trostle argues for a behavioral definition of compliance that can extend
to types of care originating outside of the medical field directly. These can be patient-
created methods of care, or other non-specialists.44
Though scholars like Haynes and Buston do not directly address the power
dynamics found within discourse of compliance, many commentators from within the
medical community advocate giving up some of medicine’s authority to examine the
lives of the patients and the reasons behind noncompliance. Fiona Ross writes that
compliance is typically the responsibility of the patient, but her research has shown a
number of issues with both the drug delivery system and professional practice that
lead to patient noncompliance.45 According to her, because of these systematic
shortfalls, it is necessary to put some of the blame for noncompliance on the part of
the medical system itself in addition to the individual responsibility of the patient.
Other commentators are more radical, echoing Trostle’s claim that compliance
becomes an ideology that asserts a doctor’s control over the patient. Speaking from
within the medical industry, Chatterjee calls compliance a “paternalistic” process that
organizes the doctor-patient relationship along the lines of a parent-child
relationship.46 Where Trostle sees this as a larger ethical issue, Chatterjee (like Ross)
is concerned with the waning health of noncompliant patients. Chatterjee advocates
for a process begun in the UK called “concordance.” This process tries to position the

79
doctor and patient as equals and insists that, “there should be an open exchange of
beliefs about medicines upon which both prescribing and medicine taking decisions
may then be based.”47 For advocates of concordance, this “open exchange” and
cooperative decision making process is meant to provide the doctor with the point of
view of the patient, illuminating potential reasons for noncompliance and possible
solutions.
What is important about concordance is not necessarily that it opens up a space
to unseat the medical gaze in its entirety. Nor does it truly reverse or remove any
expression of disciplinary power between doctor and patient. Concordance does,
however, create two changes to the techniques of care within medico-administrative
knowledge. The first is that it puts the doctor in the position of convincing the patient
of treatment rather than telling them or ordering them. The doctor holds a
responsibility for the well-being of the patient, but must also renounce a demand that
the patient’s well-being can only be achieved through the exact application of
recommendations based on clinical medical knowledge. Chatterjee, for example,
disdainfully remarks that compliance “has certain connotations, such as submitting to
and obeying instructions" with non-compliance thus regarded as “deviant behavior” by
the medical industry.48 In discourse of concordance, the doctor is still the expert and
possesses unique knowledge about the disease afflicting the patient, but the patient can
question the legitimacy of that knowledge or choose not to follow a doctor’s
recommendation presumably based on this knowledge without being labelled as
abnormal or irrational. Instead, as Chatterjee points out, “it may be sensible, safe, and

80
in the interest of the patient to be non-compliant” because of issues such as reactions
to certain drugs.49 Conrad agrees, claiming that what appears as irrational non-
compliance is often the patient’s way of asserting control over their disease.50 Whereas
clinical medicine hinges on the exclusion of “deviants” that do not follow orders, the
concordance model claims a knowledge of the truth of disease, but does not
marginalize those that disagree in the same way. Instead, clinical medicine’s idea of a
disease’s “truth” must be able to be articulated within multiple contexts that are
determined by the patient. In this way, the noncompliant patients do not become
abnormal per se, but are subjects that need to be assimilated into medical gaze by
means other than fear of adverse health effects or doctors’ direct orders. The
complicity of the patient that has always been present in clinical medicine’s use of self
care now requires that patient also understands the logic behind the recommendations,
not just follow them with an assumption that they will promote health.
The second shift that occurs through concordance is the focus on the everyday
life of the patient. The disease no longer exists only in the abstract, as in the clinical or
laboratory model, but rather as lived experience. Though medical knowledge still
originates within the clinic or the laboratory, it undergoes a shift when it encounters
the life of the patient. Compliance-based discourse assumes that the patient will order
her life around doctor’s recommendations about when to take medicine, exercise, eat,
etc. Concordance assumes the opposite: that medical recommendations will have to be
modified based on the unique situation of the patient. Certain drugs may, as in
Chatterjee’s example, cause adverse reactions to a patient. Or, as in any of Haynes’

81
examples, patients may misunderstand the treatment procedures, lack social support,
forget to take medicine, or any number of other reasons.
In both of these shifts, we see medico-administrative knowledge not only
critiquing itself in order to be understood within the context of the patient’s individual
understanding, but also opening itself up to acknowledge the existence of differences
in class, gender, and other identities that do not emerge within the laboratory or clinic.
In a study by Buabang, for example, it was found that noncompliance with
hypertension medication in Ghana came from a lack of funds to buy the medicine.51
Even Buston’s identification of “embarrassment,” difficulty with the apparatuses, and
denial as potential causes of noncompliance point to socially- and culturally-situated
factors influencing the degree to which patients follow doctors’ orders.
Diabetes care recommendations echo these issues with concordance. For
example, Robert M. Anderson, publishing in Diabetes Care, suggests five changes to
the traditional medical that will help bring patients into the fold:
1. Doctors should recognize that the patient is in control of decisions
about care; 2. Practitioners should be information sources and impart
knowledge onto the patients instead of blindly ordering them; 3.
Pejoratives like adherence, compliance, and noncompliance should be
eliminated; 4. Medical schools should train doctors as “mentor[s],
advisor[s], and coach[es]”; and 5. The patient should be made aware of
a unique patient-provider relationship that emerges from the
management of diabetes.52
These recommendations are patient-centered, but they still do not give the patient the
power to produce medical knowledge. Instead, the patient is treated as a type of
subject that can understand medical knowledge, even if they cannot produce it. By

82
hearing the rationale behind the decisions in care regimes the patient is assumed to
buy in to the process, still becoming complicit in the reproduction of the medical
gaze.
Though concordance ends up as a reproduction of the clinical medical gaze,
there are individuals working to the side of the medical field to take on concordance’s
claim to open up medical regimes of self care to account for the individual, while also
allowing the individual to produce medical knowledge about their own body. Many of
these individuals belong to a group called Quantified Self, a loosely collected group of
people who use a variety of health-tracking technologies to record aspects of their
health. Chapter Three deals in detail with Quantified Self as a larger phenomenon, but
this chapter introduces several individual projects because they are examples of a
systematic way of re-organizing health care that is beginning to gain popularity
internationally. Quantified Self presents itself less as a directive about what should be
tracked and more of a methodology on how to track. The goal is to create large sets of
data over a variety of different areas and analyze them using n=1, the assumption that
they will only apply to a single person. The projects in this chapter are limited to
diabetes-related projects, but they can include anything from tracking movement to
emotion to time spent using certain computer programs.
Doug Kanter has presented at Quantified Self meet ups and generally uses the
principles of the group. He has collected over 300 data points a day from an insulin
pump and two glucose monitors. He combines this with data about his lifestyle, such
as where he is or what he eats to create a database of information that he can access.
Kanter’s diabetes was not radically out of control and he was not necessarily

83
managing it in a way that clinical medicine would disapprove of. His motivation for
tracking came from his own desire to learn about his diabetes and how it played out in
his life. Though he was not necessarily “unhealthy” by clinical standards, Kanter
wanted to become healthier.
Kanter observes that often new diabetes patients are overwhelmed by data and
have difficulty understanding what is going on with their disease and their own
bodies.53 His main focus was on creating visualizations of his data that would draw his
attention to particular trends or potential problems with his disease that may not
emerge as clearly through more traditional methods of self care. One of these
visualizations was a circle that consisted of blood glucose measurements taken
throughout the year, coupled with how much running he was doing:

84
Figure 1: Visualization of blood glucose measurements and running
http://databetic.com/?p=304
Kanter explains the colors on this graph:
The main image shows 91,251 blood sugar readings from my Dexcom
continuous glucose monitor (CGM). Each colored line shows one day.
January 1 is at the top, with days progressing clockwise around the
circle. Lines grow longer with more readings for that day. Blood sugars
are color-coded and grouped based on the reading. I represented the in-
range readings as white to make it easier to spot the days where my
blood sugar control was not as good. High blood sugars are a colder
colors, low blood sugars are warmer.54
He also added text around this graph to note events happening in his life:

85
Figure 2: Visualization of blood glucose measurements and running, text added
http://databetic.com/?p=304
From these graphs, Kanter was able to “merge medical data and information from ‘the
rest of [his] life’”55 in a way that would be impossible through the current system of
clinical medicine because it would be too personalized and unable to fit into a body of
medical knowledge that abstracts the individual. Kanter’s visualizations subvert that
process, creating a highly individualized set of data that draws attention to aspects of
how his individual body performs the disease that could not necessarily be
extrapolated to fit every case of the disease. In Kanter’s case these data points and
conclusions centered around his running. After analyzing the data, his conclusion was
that the more he ran, the less insulin he needed, up until he was running 30 miles per
week, where the insulin dosages remained constant. After he ran a marathon and
stopped training, Kanter’s need for insulin dosages spiked dramatically. Kanter’s
instance is not part of a larger “truth” about diabetes, but an isolated finding about the
relationship between diabetes and his own body – specifically his own body as it runs

86
– that only applies to Kanter.* Moreover, and somewhat counterintuitively, this data
and the resulting conclusion focus on grounding his diabetes as a phenomenon that
exists within his body. The disease no longer becomes an abstract configuration of
glucose levels and insulin treatments, but a disease that is embedded within a body
that responds to activity in a way that can only be pinpointed by looking at data tied
to that specific body.
By collecting data and producing visualizations, Kanter disrupts the clinical
medical model in two ways. The first is that he collects data that is only applicable to
his own case and does not seek to add to a larger, abstract body of knowledge about
diabetes as a disease. Kanter’s models project information about the disease, but the
disease is taken to be a particular, embodied case that takes into account medical facts
about diabetes in general while also holding the possibility that his particular
instantiation may be different in some ways. Here the individual case is, on the one
hand, more important than the archive of knowledge about the disease. The disease
become a part of Kanter’s body, reacting to his actions, his training, and the situations
that he puts himself in. The strength of Kanter’s method lies in the fact that he records
a large amount of miscellaneous data about his life that he can then link to insulin
need. Some of this is passively recorded (such as steps taken or miles run via activity
monitors), other data is actively recorded (such as filling out a spreadsheet with
*
This is not to say that the findings are not useful to other people or that someone else could have the
same results, only that Kanter’s conclusion could not be assumed by another individual in the same way
that larger truths of diabetes can be transferred between patients. For example, laboratory medicine has
proved that insulin deficiency is the cause of diabetes, a fact that can be applied to any diabetic to some
degree.

87
location). Through this large dataset, he is able to find unexpected ways that diabetes
manifests itself in his body. The link between running and insulin need may not be
entirely surprising, but it can be found more easily through Kanter’s process than by a
clinical medical process. Clinical medical studies of diabetes typically look at
relatively sedentary individuals and do not anticipate higher-level athletes that can run
marathons like Kanter.* Even though Kanter’s process leads him to a conclusion about
his own body, his methods serve as a potential (but not authoritative) model for other
diabetes patients and the medical discourse at large. The model is presented as an
option for other patients to take and make their own, with the understanding that the
model could, and most likely will, have to be modified for each case.
Kanter’s case may seem to put control of diabetes entirely into the hands of the
patient, but this is not the case. Such a move would be a return to the pre-clinical
model of medicine that was patient-directed, but there are two reasons this is not the
case. The first reason for this comes from Foucault’s claim that early, premodern
medicine “believed that the only possible locus for recovering from disease was the
natural environment of social life, the family.”56 Moving the care of disease to the
home served to alleviate costs for the state while medical discourse posited that “in the
family, the disease was in a state of ‘nature’, that is, in accord with its own nature and
freely exposed to the regenerative forces of nature. The gaze that is turned upon it by
those close to the sick person has the vital force of benevolence and the discretion of
hope.”57 For those that had no family, the hospital was created to serve in place of the
*
Also see the case study of Felix Ming below for a more difficult-to-identify link between the body and

88
family.* In terms of Kanter’s care, the shift toward home self-care and self-
organization of life initially seems to re-introduce this idea that the home and family
is the ideal source of care. The physical space of the home is prioritized, as in pre-
clinical medicine, and both types of medicine are more economically viable for the
state, but the gaze that is levied onto the patient varies in each case. In pre-clinical
medicine, the patient’s home provides a space in which they are subject to a
“benevolent” and “hopeful” gaze of family and friends. Contemporary diabetic care
serves to reproduce medical discourse by directing the actions of the individual and
creating an individual complicit in performing those actions. The gaze at work within
Kanter’s diabetic home care does not aim to amplify the type of care present at the
home and nurture the disease by placing it within “regenerative forces of nature.”
Instead, the gaze here is one that is displaced from the clinic and serves to neutralize
the space of the home, encouraging Kanter to engage within a strict regime that
replicates the clinical setting as much as possible, even if he was partially responsible
for identifying ways that the care should be enacted. The home becomes a type of
treatment center in its own right. Within the hospital setting, the patient would, in
theory, be subject to strict dietary schedules and foods choices; made to adhere to an
exercise plan; and given pre-measured dosages of insulin where necessary. As they
exit the hospital space and move toward the home space, the patient is expected to
insulin need that emerges from this style of information gathering.
*
In The Birth of the Clinic, Foucault continues to trace how the hospital initially arose to perform these
functions but slowly shifted due to a number of forces. By the time the hospital had become an
institution, it had drastically changed from the original concept of it as a place to care for those who had
no family.

89
adhere to these same recommendations, regardless of the “natural” home state
surrounding them. Kanter still performs these types of actions and attempts to order
his home in a way that helps him manage his disease, though his actions are directed
by his own data analysis as much as by more traditional clinical recommendations.
The second and third manners that the shift of care from hospital to home
falsely appears to be a shift toward a pre-clinical medicine come from Jewson’s
descriptions of what he calls “Bedside Medicine,” the same early 18th century medical
practice that Foucault describes. Jewson describes the patient in Bedside Medicine as
an individual entity, claiming that “the vision of the sick-man institutionalized within
the tenets of Bedside Medicine was that of a conscious human totality – a viewpoint
that transcended, not merely united, the distinctions of psyche and soma found in
modern medicine." Whereas clinical medicine (occurring in the early 19th century for
Jewson) breaks apart the patient into abstract elements that can be measured and tested
with the aim of adding to a corpus of medical knowledge, Bedside Medicine focused
on the actual patient, who “appeared…in a guise similar to that in which he appeared
to himself, i.e., as an individual and indivisible entity.” The shift toward the patient as
a collection of abstracted knowledge of a disease had not yet occurred. The “person
oriented role system” of Bedside Medicine is a way of organizing where judgments
about others are made in terms of the individual attributes of persons rather than their
formal statuses, decisions being open to negotiation and discussion between the
members of the group on the basis of their particularistic ideas and interests. Members

90
attain their location in the role system through a process of mutual exploration of
personal identities.58
Kanter’s increased attention toward himself does position himself as part of a
lived environment and a unique body that exceeds absolute control of clinical
medicine. Such a configuration does bring in a notion of individuality in the sense of
being a part of a single, unique circumstance and needing a personalized type of care.
However, this is not a direct return to preclinical Bedside Medicine as Kanter is not a
“conscious human totality” beyond the purview of medical knowledge. He is situated
within a larger context of being a unique body within a unique environment and
objects that affect how care can be administered, but Kanter also exists as a
manifestation of the larger, abstract concept of diabetes. This is one of the primary
areas in which we see the Kanter and other diabetic patients as a posthuman subject
and unable to return to the same place it holds in a pre-clinical model of medicine: the
patient is intimately connected with its environment, embodied, capable of being
transferred into an informational pattern, yet able to incorporate medico-administrative
technologies based on clinical medicine such as blood glucose monitors into their
person.* Kanter, as with most contemporary commentators on diabetes care, does not
advocate for a complete break with medical care, even as he sees himself as a unique
case. Rather he insists on looking at how to manage a relationship between medical
recommendations of care, how his own body manifests diabetes, and the his own
*
For a more detailed account of what makes up the posthuman, see chapter 1

91
surroundings, acknowledging that the patient and its associated disease will always be
part of a network of other forces.
Diabetes, then, is a unique disease in the sense that it disrupts much of the
clinical model of medicine by including the individual as a source of legitimate
medical knowledge, yet it does not result in a return to Bedside Medicine by disposing
of clinical medical knowledge or the overarching medical institution. Instead, it
creates new forms of knowledge and techniques of power that radically reorganize the
patient/medical knowledge nexus. The issue of noncompliance is the primary
disruption in this model, as it shows the dual nature of the clinical medical gaze’s
attempt to regulate chronic disease. Clinical medicine must, for logistical and
economic reasons, shift the burden of care to the individual, but this process moves the
site of care away from the clinic toward a space that clinical medical discourse has
aligned with irrationality, nature, and unknowability. Such a move and re-
spatialization is an attempt to reclaim home-based self-care under the umbrella of the
medical gaze and clinical medicine’s recommendations for care. However, the lives of
the patients constantly act outside of the proscriptions of the medical gaze while still
applying some of the recommendations. Patients are often seen to be “out of control”
and frequently labelled as noncompliant, an issue that labels the patient engaging in
self-chosen everyday activities as a deviant. Alternatively, patients are advised to
realize that their own knowledge of their disease is incomplete and they should
supplement it with clinical medical discourse by “continuously engag[ing] in fresh
discussion in order to ensure that the right interventions are chosen – hereby actively

92
avoiding that provider and patient believe that they have finished discussing the
aspects of accepting, understanding and knowing.”59 Encouraging the patients to learn
is suggested with the assumption that they will seek out approved medical discourses,
but as Kanter demonstrates and the example below will reinforce, this often results in
patients working outside of clinical medicine to create their own medical knowledge
and regimes of self care that works alongside medical knowledge.
Creating these tangential medical knowledges requires a re-appropriation of
medical technologies by patients to create supplemental and alternative discourses. In
these cases, medical institutional knowledge still remains central to diabetes
management, but the patients utilize the techniques of clinical medicine to create their
own databases of information that identify the patient as an individual case.
Legitimacy of these discourses comes partially from the legitimacy of the medical
tradition that it appropriates, the applicability of those discourses to everyday life
situations that are often not accounted for by clinical medical recommendations, and
the ability of the technologies to identify ways that the patient’s body operates in a
unique fashion. Here, the archive of information collected by the patient serves not to
add to a larger body of knowledge on the disease, but to create a singular instance of a
diseased patient that may or may not apply to other cases.*
*
As in Foucault’s concept of clinical medicine or Jewson’s laboratory medicine, whereby medical
practitioners perform research to create a map of a disease that exists outside of the individual case
within a patient.

93
One instance of this tendency can be seen in Vivienne Ming’s efforts of
tracking her son’s diabetes.* Like Kanter, Ming is loosely connected to Quantified Self
and has presented the follow project at Quantified Self meetups. Ming is a
neuroscientist whose son has Type 1 diabetes. When she found out about her son’s
disease, she and her husband began to use their training as scientists to attempt to help
their son, Felix. To do this, they tracked and recorded various parts of his life,
including what he ate, his activity levels, blood glucose levels, etc.60 Felix was hooked
up with a Dexcom continuous glucose monitor, Omnipod insulin pump, Fitbit
accelerometer, and Basis activity/heartrate monitor.61 She then took a spreadsheet with
this information to her son’s doctor, who refused to take the data and said that it would
be impossible for Ming to interpret the data about the disease because it is
endocrinology, a realm of medical knowledge inaccessible by anyone other than a
specialist.
The initial encounter between Ming and her doctor becomes an encounter
between: (1) the possibility of legitimate interpretation of medical data by a patient
that can account for a single, unique instance of a disease without assuming it to be
an exact replica of the disease writ large and (2) clinical medical discourse’s twin
goals of helping the patient while also reserving the ability to interpret medical
knowledge and requiring the patient to submit to the medical gaze for care. The
doctor views the
*
Vivienne Ming - Tracking My Son's Diabetes on Vimeo. vimeo.com. Web. 14 Jul. 2014.
<http://vimeo.com/81272562>. The examples here are come primarily from Quantified Self (QS) talks,
though many individuals have been using these methods since before QS existed. For the purposes of
this paper, QS is seen primarily as a rallying point for individuals already managing care in a particular
way. The following chapter will engage in a more in-depth analysis of QS itself.

94
disease as impermeable to untrained vision. Only the medical gaze can unearth the
secrets behind it. As in Foucault’s clinical medicine and Jewson’s Hospital Medicine,
the doctor views Felix’s case not as a unique patient with a disease, but as an instance
of the disease that can only be identified and treated by the doctor.62 Without access to
the knowledge of clinical medicine, Ming cannot properly understand the disease,
even though she can see the patient herself. But what is especially interesting about
this case is that Ming’s data is collected according to a process of clinical medicine.
She adhered (at least loosely) to scientific standards of data collection and presented
the data in a format that should have been recognizable to the doctor. Her data was
rejected not necessarily because the format was illegitimate according to medical
standards, but because the data applied only to a single patient and could not be
understood within the framework of clinical medicine that requires the patient to be a
non-unique instance of a disease. Further disqualifying the data, it was also collected
outside of a unbiased clinical setting. By injecting the patient back into the medical
data, it made the data illegitimate in the eyes of medical discourse. No absolute “truth”
of diabetes could be discerned from Ming’s data, so clinical medicine would not
consider it as legitimate material for analysis. But for Ming – and many individuals
currently undergoing treatment for chronic illness – the “truth” of the disease and the
ability to understand it does not lie within an archive of clinical knowledge, but within
data collected from the individual instance of the disease as it is present within Felix.
It is not necessary to be trained in endocrinology in order to see the disease, only to be
attentive to various aspects of how the disease affects the child’s life. For Ming and

95
her husband, it is possible to act outside of medical discourse and engage with some
sort of “truth” of the disease.
This truth ended up to be particular to Felix’s case and not necessarily
applicable to other cases of diabetes, a quality that goes directly agains the medical
truths uncovered by clinical medical knowledge, which seeks to institutionalize facts
about the disease in general. Though the data Ming and her husband was not accepted
by their doctor, they continued to collect data and look for ways that it could figure
into treatment plans for their son. The most drastic way that they used this data was to
create a model for insulin injections that was particular to Felix and his daily habits
and the way that Felix’s stress hormones interacted with his diabetes, not necessarily
in line with the recommended program the doctor suggested.63 Over several years,
they were also able to point out environmental factors that affected Felix’s blood
glucose that would not have been caught by traditional clinical models. In one case,
Felix’s readings were showing high blood glucose following breakfast on weekdays
caused by the anxiety of going to school. Traditional clinical models of care would
have only caught the readings of high blood glucose following breakfast as a general
pattern and been unable to link it to his body’s processing of anxiety of going to
school. Ming and her husband were able to modify their model of insulin dosages to
account for the specific stress of going to school and the needs of Felix’s body.
Whereas traditional clinical models would attempt to extend this link between stress
and blood glucose levels to all diabetics, the Ming’s data analysis can only apply to
Felix.

96
Ming’s case demonstrates a way in which diabetic patients take the
technologies of clinical medicine and use them in a way that reforms clinical
knowledge to take into account the patient as an entity within the context of everyday
life. The data that Ming collects uses the processes of medicine and engages with the
larger body of knowledge, but creates an individual data set that forms a unique
knowledge of a singular patient. Felix still goes to the endocrinologist and still uses
insulin therapy, a treatment that originates in clinical and laboratory medicine, but that
insulin is administered on a schedule set by Ming based on the data collected about
how Felix’s body interacts with his diabetes. Ming is able to construct her own system
of truth from the data and tests that she and her son conduct that works alongside the
larger system of medical discourse. The findings that Ming, Felix, and her husband
come across add to an archive of possible truths for various instances of the disease,
but do not (as in clinical medicine) serve to add to an abstract and objectively factual
archive of medical knowledge. Ming shares her results through talks, but not to
demonstrate that her method or her findings are always applicable to every case of the
disease. Instead, she looks to show an individual case – that still refers to the sum of
cases of the disease – that may provide a clue for another patient seeking to enact a
treatment plan.
Here we see a reconfiguration of power as the medical gaze is questioned by
the patient’s practices of self-care outside of the clinic. As Ming demonstrates,
patients who engage in self care can now create modes of treatment that run alongside
and interact with medical discourse, rather than reproducing them directly.

97
Enforcement of these treatments occurs on the level of the individual and the self,
away from the direct oversight of the clinic, allowing these alternative treatments to
take root within the lives of individual patients.
Both Ming and Kanter create their practices of self-care within a gap in the
medical system previously occupied by discourses on noncompliance and
concordance. As clinical medicine required that individuals take on more
responsibility managing their own disease, it became evident that even well-intended
application of disease management recommendations were difficult to put into
practice. Patients with chronic diseases like diabetes were recommended strict control
of their self-care regimes. Diabetic patients were told by the American Diabetes
Association to practice strict control over their diet, exercise, blood glucose levels,
and insulin administration, regardless of their type of diabetes. Not only was the
efficacy of this recommendation questionable, many patients could not practice the
desired level of strict control because of a lack of knowledge, busy schedule, lack of
access to materials, unexpected bodily reactions (e.g. scarring over an injection site,
unresponsive fat cells, odd levels of hormones from anxiety or sadness, etc.), or any
number of other factors.
These patients were initially labelled noncompliant and told to regain control
over their treatment regimes or face the dangerous possibility of failing health through
complications with their disease. Concordance, a newer model, sought to bring
patients back into the fold by providing them more information about the rationale for
certain treatment regimes. As noted above, though concordance tried to relate to the

98
patient as an individual through a more compassionate provider, this model served to
only reproduce the medical gaze within patients and failed to fully re-work a system
of medical knowledge that could account for a patient with unique circumstances.
In between a medical model of care that required the individual to take on
more responsibility for care and an embodied, lived experience that often disrupted
attempts to perform those recommendations, Kanter and Ming developed their
processes of self-tracking and self-care. From the perspective of medical knowledge,
they appeared noncompliant by refusing some medically-sanctioned regimes of care
in favor of finding their own. However, by utilizing scientific data gathering and
medical technologies, they were able to produce knowledge about their diseases that
was not completely outside of clinical medicine. When Kanter adjusted his insulin
levels according to how much he was training and when Vivienne Ming adjusted Felix
Ming’s insulin administration in response to anxiety levels, both did so in order to
keep their blood glucose levels within clinically-approved ranges. Here, Ming and
Kanter have given legitimacy to their noncompliance in medical terms; by generating
knowledge about their disease to find their own technique of self-care, they have
maintained control over their disease.
These two examples no not just reorder methods of self-care, but do so by
reorganizing the model of the human that acts as the foundation for medical
recommendations of self-care. As noted above, clinical and laboratory medicine rely
on a concept of the human where individuals bodies matter less than a generalized
archive of knowledge about humans in general. Individual humans are compared to

99
this archive in order to diagnose any abnormalities or disease. However, in Ming and
Kanter’s case, their tracking procedures allow them to create a localized idea of their
own embodied situation. Such a model is able to take into account specific aspects of
their body (hormones released by anxiety, insulin absorption with regard to training)
and environment (how school affects anxiety, which affects blood glucose levels) –
aspects that could not be accounted for within a more traditional model of clinical and
laboratory medicine.
Moreover, projects like those of Kanter and Ming do not assume that the exact
ways that the bodies operate are completely known. Only by collecting data can the
operations of the individual body emerge and, even then, those insights are continually
tested through data collection. Ming’s case exemplifies this most strongly, as the
initial reason Vivienne began data collection was an unexpected drop in glucose levels
in Felix’s blood. Emphasizing the body in this manner reflects a type of subject acts
against the humanist model, refusing to take consciousness as the central characteristic
of being human and does not assume a completely knowable self.64 Instead, these
projects begin to create a type of subject that appears most posthuman because it can
learn more about itself by integrating tracking technologies into its body, whether by
removable devices like FitBits or through invasive devices like continuous glucose
monitors.* Much like the criticism of posthumanism in chapter 1 has pointed out, the
*
There are two different ways to view this. The first is through Hayles’s claim that technology can be
articulated seamlessly with the body (Hayles, N Katherine. How We Became Posthuman: Virtual
Bodies in Cybernetics, Literature, and Informatics.: University of Chicago Press, 1999. 2-3.). This will
be analyzed in detail in the following chapter, but the initial assumption is that there is a significant link
between the body and the data recorded on a tracking device. Consistent data is believed to give a

100
figure of the human is still retained in the projects of Ming and Kanter, even if it is not
based explicitly on consciousness or a single, abstract concept of “the human.” Even
so, care is radically re-worked to open up space for patients to participate in the
knowledge-creating process and directing their own self care. The next questions that
emerge are: (1) whether this type of knowledge creation can be expanded to instances
of subject formation outside the medical field and (2) whether this process can indeed
bring about a renewed interest of ethics, justice, and critique even though it fails to
completely discard the human.
Chapter three looks at several different instances of Quantified Self projects
that, like Ming and Kanter, track various metrics to monitor one’s health. Unlike Ming
and Kanter, these Quantified Self projects involve managing more general aspects of
well-being that are tied to clinical medical recommendations, but also exceed them.
These include finding ways to sleep better, keeping Myasthenia Gravis under control,
and increasing overall happiness. The chapter will claim that in each of these cases, it
is possible to see technologies usually used to control populations being applied on the
individual level: a form of biopower that does bring the methods of subject formation
representation of the body that can be manipulated and analyzed to learn more about the workings of
the body.
The second view is one of Objected Oriented Ontology or Speculative Realism. In this view, as noted in
chapter 1; Roden, David (2014-10-10); Posthuman Life: Philosophy at the Edge of the Human (Kindle
Locations 735-737); and Taylor and Francis. Kindle Edition, the objects present a different type of
ontology about the world. The data presented would be a glimpse into how those technologies configure
the world. According to the Object Oriented Ontologists and Speculative Realists, we would not,
strictly speaking, be understanding a new ontology of the world by looking at this data, but interpreting
it and appropriating it for human use. This would be to take a function view of Objected Oriented
Ontology and Speculative Realism that still includes the human within the interpretative process, as
with the critiques brought up in chapter 1.

101
identified in this chapter outside of dealing with exclusively chronic disease. Chapter
four will address how this type of subjectivity operates within institutions to begin to
address the second question posed above concerning issues of justice, ethics, and
critique.
1
Michel Foucault. The Birth of the Clinic; An Archaeology of Medical Perception: New York,
Pantheon Books, 1973. Print. 34.
2 See:
Angell, Marcia. "Caring for Women's Health -- What Is the Problem?" The New England Journal of
Medicine 329 (July 22, 1993).
Geary, Mary Ann. "An Analysis of the Women's Health Movement and Its Impact on the Delivery of
Health Care Within the United States." Nurse Practitioner 20.11 (November, 1995): 24-35. Print
Ruzek, Sheryl. "Towards a More Inclusive Model of Women's Health." American Journal of Public
Health 83.1 (January, 1993).
3 Angell
4
"Diseases and Conditions: Diabetes." Mayo Clinic. Web. <http://www.mayoclinic.org/diseases-
conditions/diabetes/basics/definition/con-20033091>.
5
"Diabetes A-Z." National Institute of Diabetes and Digestive and Kidney Diseases. Web.
<http://diabetes.niddk.nih.gov/dm/pubs/overview/index.aspx#managed>.
6 "Diabetes A-Z."
7 "Diabetes A-Z."
8
"The Effects of Insulin on the Body." Healthline. Web. <
http://www.healthline.com/health/diabetes/insulin-effects-on-body>.
9 "Diabetes A-Z."
10
"Diabetes and Hypoglycemia." Diabetes.co.uk. Web. <http://www.diabetes.co.uk/Diabetes-and-
Hypoglycaemia.html>.
11 "Diabetes A-Z."
12
Poretsky, Leonid. Principles of Diabetes Mellitus. N.p.: Springer, 2010.
13
MacCracken, Joan, Donna Hoel, and Lois Jovanovic. "From Ants to Analogues: Puzzles and
Promises in Diabetes Management." Postgraduate medicine 101.4 (1997): 138-150. 138.
14
Davis, Matthew R. "Biomedical Control and Diabetes Care." Science as Culture 7.1 (March, 1998):
69-93. CrossRef. 72
15 Davis 72
16
Armstrong, David. "The Rise of Surveillance Medicine." Sociology of Health and Illness 17.3
(1995): 394. Also see Foucault Birth of the Clinic 88-105.
17
Foucault Birth of the Clinic 59
18
Foucault quote from Wolfe, Cary. "What Is Posthumanism?" Journal for Critical Animal Studies
IX.1/2 (2011): 235-241. Print. 53.
19 Wolfe 53
20 Davis 74
21 Davis 74
22 Davis 74
23 Davis 74
24 Davis 76-77
25
Armstrong 393. It is also worth noting that Foucault does not use this term, though he does describe a
similar process.
102
26
History of Insulin - Discovery to Modern Day Timeline. www.diabetes.co.uk. Web. 13 May 2016.
<http://www.diabetes.co.uk/insulin/history-of-insulin.html>.
27
Jewson, N D. "The Disappearance of the Sick-man From Medical Cosmology, 1770-1870." Int J
Epidemiol 38.3 (June, 2009): 629
28 Jewson 629
29
Foucault Birth of the Clinic 9
30 Davis 81
31
Ferzacca, Steve. ""Actually, I Don't Feel That Bad": Managing Diabetes and the Clinical Encounter."
Medical Anthropology Quarterly 14.1 (2000): 29
32 Davis 85
33
"DCCT and EDIC: The Diabetes Control and Complications Trial and Follow-up Study." National
Diabetes Information Clearinghouse Print. <http://www.niddk.nih.gov/about-niddk/research-
areas/diabetes/dcct-edic-diabetes-control-complications-trial-follow-up-study/Documents/DCCT-
EDIC_508.pdf>
34
Anderson, Barbara, Joyce Ho, Dianne Finkelstein, and Lori Laffel. "Parental Involvement in Diabetes
Management Tasks: Relationships to Blood Glucose Monitoring Adherence and Metabolic Control in
Young Adolescents with Insulin-dependent Diabetes Mellitus." The Journal of Pediatrics 130.2
(February, 1997): 257-265. Print.
35
Borus, Joshua, and Lori Laffel. "Adherence Challenges in the Management of Type 1 Diabetes in
Adolescents: Prevention and Intervention." Curr Opin Pediatr 22.4 (August, 2010): 405-411. Print.
36
See Trostle, James. "Medical Compliance As An Ideology." Soc Sci Med 27.12 (1988): 1300. Print.
for an overview of Robins, Bissonette and Seller, and Haynes on the history.
37 Trostle 1302
38 Trostle 1300
39
For example, see Haynes, Brian, Elaine Wang, and Marleide da Mota Gomes. "A Critical Review of
Interventions to Improve Compliance with Prescribed Medications." Patient Education and Counseling
10 (1987), Buabeng, Kwame. "Unaffordable Drug Prices: The Major Cause of Non-compliance with
Hypertension Medication in Ghana." J Pharm Pharmeceut Sci 7.3 (2004), Buston, Katie, and Stuart
Wood. "Non-compliance Amongst Adolescents with Asthma: Listening to What They Tell Us About
Self-management ." Family Practice 17.2 (2000), Claydon, Bridget, and Nathan Efron. "Non-
compliance in General Health Care ." Opthal. Physiol. Opt. 14 (July, 1994), Cockburn, Jill, Robert
Gibberd, Alexander Reid, and Robert Sanson-Fisher. "Determinants of Non-compliance with Short
Term Antibiotic Regimens ." British Medical Journal 295 (October 3, 1987), Dimatteo, Robin.
"Depression Is a Risk Factor for Noncompliance with Medical Treatment." Arch Intern Med 160 (July
24, 2000), and Ross, Fiona. "Patient Compliance—Whose Responsibility?" Soc Sci Med 32.1 (1991),
though this is just a small sampling of the literature on noncompliance.
40 Haynes 155
41 Haynes 155
42 Buston 136
43 Trostle 1305
44 Trostle 1306
45 Ross 94
46
Chatterjee, JS. "From Compliance to Concordance in Diabetes." J Med Ethics 32 (2006): 509.
47
Chatterjee 509. Also see Bissell, Paul, Carl May, and Peter Noyce. "From Compliance to
Concordance: Barriers to Accomplishing a Re-framed Model of Health Care Interactions." Social
Science & Medicine 58 (2004) and Campbell, R, M Evans, M Tucker, B Quilty, P Dieppe, and J.L.
Donovan. "Why Don't Patients Do Their Exercises? Understanding Non-compliance with
Physiotherapy in Patients with Osteoarthritis of the Knee." J Epidemio Community Health 55 (2001):
for other, very similar, arguments in favor of concordance.
48 Chatterjee 509
49 Chatterjee 509
50
Conrad, Peter. "The Meaning of Medications: Another Look at Compliance." Soc Sci Med 20.1
(1985): 36
51 Buabang
52 Anderson 415
103
53
Doug Kanter - A Year of Diabetes Data on Vimeo. vimeo.com. Web. 14 Jul. 2014.
<http://vimeo.com/79837532>. 12:35
54
Doug Kanter - A Year of Diabetes Data
55
Doug Kanter - A Year of Diabetes Data
56
Foucault The Birth of the Clinic 39}
57
Foucault The Birth of the Clinic 39-40
58 Jewson 625-26
59
Brok-Kristensen, Mikkel. "Changing Diabetes Care for Good." EPIC (2007): 99
60
Vivienne Ming - Tracking My Son's Diabetes on Vimeo. vimeo.com. Web. 14 Jul. 2014.
<http://vimeo.com/81272562>. 1:25
61
Vivienne Ming - Tracking My Son's Diabetes 4:00
62
Foucault Birth of the Clinic 59
63
Vivienne Ming - Tracking My Son's Diabetes 3:18
64
See Castree, Noel, Catherine Nash, Neil Badmington, Bruce Braun, Jonathon Murdoch, and Sarah
Whatmore. "Mapping Posthumanism: An Exchange." Environment and Planning A 36.8 (2004): 1345
for this definition of humanism.

CHAPTER 3
Biopower and Quantified Self
As the previous chapter demonstrates, when patients engage in techniques of
self-care for chronic conditions like diabetes, they often stray from the explicit orders
of medical professionals. Patients often fail to understand medical recommendations,
use methods of care from non-medical sources, or simply just forget some of the steps.
Some patients, like Doug Kanter and the Ming family take the data collection
techniques of clinical medicine and create medical truths about a disease that apply
only to a single patient. In doing so, these patients also reconfigure the humanist
attempts of clinical medicine to create the factors that comprise “the human” into an
attempt to create “a human” with its own unique characteristics and sense of self-
assessment. When this process happens, the techniques of data gathering used in
medicine are reconfigured for use by a single patient, rather than “patients-in-general”.
With the shift in focus from large-scale patient groups to single individuals, the power
relations between medical institutions and individuals undergoes a large shift as well.
The underlying organization of practices in these projects involves navigating
(1) institutional knowledges that form the basis of recommendations for how
individuals order self-care and (2) how individuals put those knowledges into practice.
As shown in the previous chapter, patients do not completely replicate institutional
recommendations, but they also do not work completely outside of them, either.
Patients submit to self-care protocols largely because they desire to increase their
health. Willing engagement with self-care techniques creates a situation whereby
104

105
individuals become complicit in reproducing the larger institutional structures of
medical knowledge. The concept of “biopower” can be useful to understand this
designation. First popularized by Michel Foucault, this model claimed that institutions
aim at regulating populations by focusing on the body and overseeing large trends in
health-related data via “biopolitical” institutions like the state and clinical medicine.*
By gathering large amounts of data on populations, a normate model of a citizen or
human could be created. This normate model was reproduced in individuals not
through the threat of violence, but through a desire on the part of the individual to be a
healthy person.
Biopower worked alongside disciplinary power, but at a macro level. This
technology centered on caring for life, but often to the exclusion of other forms of
life. Contemporary self-tracking technologies used for self-care in chronic patients
fall very much into processes, creating large quantities of data to be analyzed in order
to construct the idea of a norm. Unlike 20th century expressions of biopower, however,
these self-tracking technologies do not attempt to exclude individuals from the larger
social or political sphere based on whether or not they contain particular
characteristics found in “normal” humans. Instead, the analysis of a single person over
time forms the idea of the “norm,” allowing biopower to operate diachronically on an
*
This chapter will focus on Nikolas Rose and Paul Rabinow’s extension of Foucault’s concept of
biopower because they are working from a standpoint that includes medical and scientific iterations of
biopower. Other thinkers, however, have significantly developed theories of biopower in other areas.
The most notable include Giorgio Agamben (in Homo Sacer) and Michale Hardt and Antonio Negri (in
Empire). These scholars do not appear in this dissertation because they focus more on the application of
sovereignty (Agamben) and biopolitics’ intersection with capitalism (Hardt and Negri), which are to the
side of the discussion. Further work could be done as to how self-tracking technologies develop

106
individual with many facets rather than synchronically on a population with many
individuals.
The practices of scientist Larry Smarr illustrate of how self-tracking
technologies can be used on the individual level rather than just at the level of the
population, reorganizing how biopower plays out. In the early 2000s, Smarr wanted to
lose weight, even though he was within acceptable and clinically established ranges.
He decided to do this through the traditional method of counting calories and
exercising, but also used newer technologies, some of which are widely available on
the consumer market and some that required his special access as director of the
California Institute for Telecommunications and Information Technology at UC San
Diego. For months, he used an accelerometer called a FitBit to track how many steps
he took a day, which allowed him to figure out how many calories he burned.1 He also
recorded what he ate and tried to balance out protein, carbohydrates, and fat while
making sure his caloric expenditure exceeded his caloric intake. With such minute
tracking and all factors apparently accounted for, he should have been losing pounds
quickly. But, the results did not match up to the expected outcome and his body
wasn’t responding in the way that it should have been. He was losing weight, but not
nearly the amount that he should have lost, according to his calculations and what
would be considered typical according to contemporary medical recommendations.
Smarr believed there was an unaccounted for variable and he began experimenting to
find out what that variable was.
sovereignty and capitalism, especially taking into account some of the issues brought up in chapter four

107
Knowing he was pre-diabetic, Smarr began to monitor his blood to check for
abnormalities. He soon noticed that he had high levels of C-Reactive Protein, a protein
that rises in response to inflammation and a marker that his body was constantly
inflamed. Though this wasn’t the answer to Smarr’s weight loss issue, it was an
indication that something outside of the expected was going on inside his body. He
then began to monitor his stool for various nutrients and had his DNA analyzed to see
if he was at risk for any particular diseases that may not have surfaced yet. Eventually,
Smarr’s data showed that not only was he was at risk for Crohn’s disease, but that it
may have already started to manifest itself even though he experienced no symptoms.2
Wanting to fix the problem before it became a serious condition, Smarr took his
findings to the hospital and discussed the possibility of having Crohn’s with his
doctor. Because he had no symptoms and was functioning “normally” at the time, he
was told to come back when he noticed actual symptoms. Several weeks later Smarr’s
symptoms began to appear and subsequent trips to a new doctor resulted in a
confirmation that he did indeed have Crohn’s disease.
Smarr’s case may have ended in a successful diagnosis before the onset of
symptoms, but critics warn that constant self-analysis is not necessarily always a good
thing. H. Gilbert Welch, professor of medicine at the Dartmouth Institute for Health
Policy and Clinical Practice has observed that with enough data, anyone can find
something wrong with themselves. Welch compares Smarr’s self-tracking with a
recent trend where people would order and analyze their own full-body CT scans.
of this dissertation.

108
Most of these individuals found something “wrong” with them that would encourage
them to take action on a non-symptomatic condition.3 For Welch and other critics,
forecasting health issues from data carries the risk of unnecessary and costly surgery
and interventions, potentially damaging a patient’s health to solve an issue that might
not even manifest itself. He calls for people to recognize that “abnormality is normal,”
meaning that no actual example of the normate model of the human exists – every
body will be a variation on it.4
Though Welch remains skeptical of projects like Smarr’s, self-tracking
projects and the idea that “abnormality is normal” are indications of a shift in how
clinical medicine operates. Smarr was able to construct a set of data similar to the
type of datasets that create an idea of a normate, healthy human. By using
technologies that were, in the past, only applied to populations, he is able to create
health metrics for only his body. Smarr’s body may be “abnormal” with respect to the
population at large, but by collecting a large enough dataset, he can find regularities
within that abnormality and create a picture of how his body operates over time. For
example, at the beginning of his process, he tracked his eating habits and his
movement over time to create a picture of what a typical day would look like.
Movement and food intake over a single day mattered less than it did over the course
of time. Additionally, creating a model of eating and movement that could be applied
to anyone was not the goal, even though statistical analysis and a “norm” was Smarr’s
focus.
Smarr first compared the data he collected on himself to what normate
individuals can expect to lose when they eat less calories than they expend. Finding

109
this model of the individual inapplicable to his situation, Smarr looked to other areas
that he could track to figure out what was going on. By analyzing his blood and stool,
he was able to again create a picture of his bodily operations over time that served as a
baseline for comparison, rather than using a more typical model established by
medical studies across populations. When Smarr’s doctor failed to identify the
disease, the tension between institutional practices that look at the individual patient in
relation to a norm created from a population and a medicine of the patient that creates
a norm from a set of data originating within the individual becomes apparent. The
doctor was unable to identify the disease because the model of a Crohn’s patient could
not account for someone who is about to show symptoms, whereas Smarr’s model
could show how his body was beginning to deviate from its own normalized state.
Smarr may have taken his self-tracking tendencies to the extreme by
measuring his activity and his nutrient and protein levels, but his experience presents
an example of a growing trend where people monitor aspects of themselves to create
an archive of knowledge about themselves that can be interrogated. By taking a wide
approach to recording various markers such as nutrient density in stool, levels of
protein in blood, caloric intake, and daily activity, Smarr constructed a set of data
about himself that allowed him to identify and reconfigure not just how he used
healthcare, but how he engaged in practices of self-care. Instead of going to the doctor
with a symptom, he went with a set of data that gave an even more complete picture
of how his body operated as an intricate system. The markers and signs that Smarr
used in his diagnosis were ones that demonstrated what could be gathered through a

110
technological filter: how many steps he took, how much C-Reactive protein was in his
blood, how many calories he was consuming. Smarr was able to observe himself
through the lens of technological data-gathering as a subject that could always
potentially be sick and in need of care. Moreover, Smarr’s collection of data only
applied to himself. Unlike clinical medicine’s research on disease that constructed an
idea of an abstract disease that could manifest itself in a particular patient, Smarr’s
data could not necessarily be extrapolated to apply to anyone else. His dataset served
to create a picture of himself as always unhealthy (much along the lines of Welch’s
criticism), but in unique ways that would not necessarily be found in others. Such a
configuration is in stark contrast to clinical medicine’s method of dealing with
knowledge about patients and disease that assumed a diseased and unhealthy state
could be fixed, returning a patient to a normate state of health.
Alongside Smarr, a number of similar self-tracking evangelists operating
outside the boundaries of clinical medicine have emerged and gained considerable
attention in the media. The rise in self-tracking has been covered by news outlets such
as the New York Times, the Economist, and Vanity Fair, while also producing a TED
Talk and countless blog posts.5 The most visible manifestation of these movements is
the group Quantified Self, created by Wired editors Kevin Kelly and Gary Wolf.
Quantified Self (QS) began with the emergence of smaller and cheaper self-tracking
devices such as wearable Bluetooth-enabled accelerometers, wireless body fat scales,
and mobile phone apps. With these new tools, it was possible to track exactly how
many steps someone took in a day or to record exactly how many calories were

111
consumed and then look at that data over a large period of time to find trends. Wolf
and Kelly began to organize meet ups where self-trackers would assemble and share
stories about how their lives had changed through self tracking.
Some of these stories are as simple as tracking whether or not regular coffee
consumption helps with concentration.6 Other stories are more epic, as in the case of
Sky Christopherson, an elite cyclist who noticed that he was having increasing
difficultly recovering from his training. By tracking his sleep over the course of
several months, he realized that the temperature of his room was causing him to get
less deep sleep, an important aspect of sleep for building muscle. He wouldn’t sleep
as well in the summer as he did in the winter. Even though the fluctuation in
temperature was only a few degrees and the change in total deep sleep time was
gradual over the course of a few months, plotting the data on a graph provided a clear
indication of the issue. After looking at this data and coming to this conclusion,
Christopherson purchased a pad that could be placed on his mattress to decrease the
bed temperature to 66 degrees. His sleep improved and so did his training,
culminating in a world record some months later.7 Like Smarr, Christopherson’s
results produce a unique subject that needed to “fix” a health-related problem by
collecting data.
The informal slogan that Kelly and Wolf came up with to explain their
movement was “self-knowledge through numbers.”8 Finding out more about what it
means to be a “self” means sifting through measurable data and numbers that are
recorded through technological apparatuses. Though QS binds itself to data and
numbers in this way, calling it quantification is somewhat misleading. The movement

112
has “quantified” as one of the two words in the name, but quantification does not
happen in QS according to the same usage in the hard sciences. Quantification here
operates by collecting data and plotting it in different ways in order to observe a
pattern, but the process is very loose. The data does not have to be collected according
to hard science standards or even be repeatable by another experiment or another
person. These are not experiments that necessarily adhere to the scientific method or
produce “knowledge” that is objective, absolute, or universal.
For the QS movement, though the data is not collected according to strict
standards of rational inquiry, the “self” still becomes coterminous with the data
collected about that self through technology. For example, Smarr first attempted to
lose weight by counting calories and macronutrients and comparing his findings to
calories burned as recorded via an accelerometer. He then began to record numerical
data about the levels of nutrients and the presence of various proteins that he retrieved
by running his stool and blood through a series of tests that looked for certain
markers. Christopherson created graphs of deep sleep versus ambient room
temperature as recorded through the Zeo, a sensor attached to a headband that he wore
while he slept.9 What started as a feeling of unhealthiness in Smarr and fatigue in
Christopherson made its way into numbers before revealing an aspect of themselves
(Crohn’s disease) or their environment (the temperature in Christopherson’s room)
that required modification. The data is not gathered for the purpose of large,
statistically significant experiments or to find a scientific insight into humanity as a

113
whole.* Nor is it thrown out if it doesn’t meet the standards of a “proper” scientific
experiment since the accuracy of the data as an objective mirror of a reality is less
important than the consistency over time. The data is highly individualized to find
some aspect of the individual that has yet to express itself.
Wolf describes this aspect of QS as “the macroscope applied to the individual
human,” where data collected from as many facets of life as possible can be applied to
a single individual without needing to be justified as being important or relevant to
everyone.10 He points out that “within the ’n=1’ of the individual is an ’n=∞’ of times,
actions, and places.”11 This means that a single person is statistically significant
enough to be the basis of unlimited conclusions about that individual without needing
to reference studies done on populations. The individual here does not become one
instance of a population trend (as in traditional medicine), but the intersection of
multiple different identities and traceable actions that happen over the course of time.
QS is unique because it takes scientific methods of investigation that would usually
apply only to large-scale studies and tailors them to a single person, focusing on the
individual’s unique, yet measurable aspects, rather than the individual’s similarity to
or deviance from the statistical norm. The “human” is no longer constructed as a
uniform entity that adheres to certain statistically significant and medically-
legitimized characteristics, but an individual and embodied entity that can be
examined from multiple viewpoints.
*
Though in tools like the FitBit accelerometer and the Zeo sleep monitor, user data is collected into a
larger pool that is used for research. The implications and use of this will be discussed below.

114
By eliminating a generic idea of the human, QS is also able to bring out a
potential process for reducing normative ideas of what being human means. Smarr is,
in one sense, abnormal because he cannot lose weight through decreasing calories as
should be expected of a “typical” human. But at the same time, this designation does
not come with the assumption that he must be somehow made “normal.” Here a
“norm” becomes a starting point for an individual to assess their own situation and,
potentially, come up with different conclusions that might differ from those of a
medical professional. The abnormal/normal divide becomes less relevant because the
goal is to find out how an “individual operates within the world” and to create a set of
data that only applies to a single entity, not create universal characteristics for
individuals to exemplify. The relationship between abnormal and normal is changed
so that the normal does not become a teleological ideal, but a suggested entry way
into exploring an individual’s subjectivity. For example, Christopherson does not
have a sleeping problem that has to be medically diagnosed and treated according to
what is “normal,” but reacts to environmental temperature in particular ways that can
be modified according to specific goals (in this case breaking a world record). The
findings of Smarr, Christopherson, and others do not become integrated into a general
institutional knowledge of what it means to be human or into a large archive of
knowledge about a specific disease. QS actively disrupts the tendency to institute the
concept of a “healthy man” as the ideal subject that Foucault has identified in modern
medicine.12

115
Though a large focus of QS projects seem to enact a disciplinary mode of
power by increasing self-surveillance and internalizing certain practices of self-care, it
would be more accurate to say that these projects are an instance of biopower applied
on the individual level rather than the population level. Foucault initially discussed
biopower in volume 1 of The History of Sexuality, claiming that it arose in the late
seventeenth and eighteenth century as a procedure of power that
focused on the species body, the body imbued with the mechanics of
life and serving as the basis of the biological processes: propagation,
births and mortality, the level of health, life expectancy and longevity,
with all the conditions that can cause these to vary.
Rather than necessarily being a negative aspect of power, biopower’s purpose was “to
invest life through and through”. QS fits well within these parameters as the main
directive is to quantify the different operations of the body. Like Foucault’s notion of
biopower, QS looks at the mechanics of life behind a body, seeking to form
numerical, quantifiable datasets about the level of particular aspects on one’s health
and the surrounding conditions that cause those health conditions. Many QS projects
are concerned with helping the individual to live healthily and to promote life within
the individual, just as biopower’s aim is to “foster life.”13 Within QS, however, the
scope of the data collected is limited to the individual body by compressing
technology and data processing techniques that are typically applied to larger
populations with the goal of finding universal characteristics about that population’s
health.
For Foucault, biopower created a new dynamic between the individual and
governing institutions called biopolitics, whereby biopower became integrated into the
operations of administrative institutions. The sociologist Nicholas Rose and

116
anthropologist Paul Rabinow are two of the major scholars that have worked on
developing the concept of biopower. Rose’s work revolves around the intersection of
science, governance, and human identity, of which biopower plays a significant role.
Rabinow’s work focuses on knowledge production, ethics, and reinventing
anthropology. He has become on of the preeminent commentators on Foucault,
especially in the area of ethics. Though they each have written independent works,
their collaborative work on biopower has taken the sketch provided by Foucault and
expanded it into a much more developed concept that applies to contemporary
workings of power, especially in the ways that medicine and governance overlap.
Rose and Rabinow explain the shift toward biopower by claiming that “every
citizen must now become an active partner in the drive for health, accepting their
responsibility for securing their own well-being” while at the same time these “health-
related aspirations and conduct of individuals” is governed at a distance by
institutions.14 These governing bodies include governmental, social, medical, and
other administrative institutions that have the capability of directing the life of
individuals.
For QS, this process is not completely ejected, but it is significantly changed.
By looking at case studies of Quantified Self projects, it is possible to demonstrate
how people within Quantified Self exemplify the type of biopower that Rose and
Rabinow develop, while also reducing biopower’s scope to the individual level rather
than reproduce biopower at the population level. As shown with Smarr,
Christopherson, and with QS projects discussed shortly, there exists a strong push for

117
an individual to take on more responsibility for their own health. Smarr collected his
own data and made an early diagnosis just as Christopherson combed through his
sleep records to find potential issues with his sleep quality. However, the element that
changes with QS projects is the ability of the individual to create datasets and produce
conclusions that apply only to the individual; and this in turn calls into question the
absolute authority of governing institutions to direct care and the mechanics of life, as
those institutions do not have direct control over how life is administered. If the
medico-administrative institutions no longer have the final say in the model of a
normal patient that serves as a reference point for the patient’s own health, the
function of those institutions changes drastically. As the QS projects discussed below
demonstrate, the medico-administrative institutions may lose some of their ability to
direct self-care, but they do not disappear entirely. Rather, they continue to work with
individuals, becoming more flexible to take into account the possibility of n=1, an
individual patient that has its own markers of health and may digress from the
“normal” member of a population.
Rose and Rabinow further clarify the workings of biopower by outlining three
major characteristics: it creates truth discourses about the vital character of living
human beings; it contains strategies for intervention upon collective existence in the
name of life and health; and individuals engage in subjectification processes where
they work on practices of the self in relation to certain authoritative truth discourses in
the name of life, health, and/or the health of the population. In the first characteristic,
where biopower is said to work through truth discourses about the “‘vital’ character of

118
living human beings,” these discourses are propagated through authorities believed to
be experts on a particular subject.15 QS works in this same manner, but within a much
different scope. Much of the discourse surrounding the techniques employed by
Quantified Self occurs through presentations given by self-experimenters. QS
conferences and meetings generally have a show and tell format where presenters are
encouraged to answer three questions: “What did you do?” “How did you do it?”
“What did you learn?”16 Through these questions, the presenter appears as an expert
on a particular revelation about their own body. The findings typically revolve around
health-related discoveries that include everything from observing heart health
following heart attacks17 to creating digital representations of health metrics18 to
improving sleep.19 Likewise, the content on the official Quantified Self website
generally takes the form of videos by Quantified Selfers explaining their projects and
their findings along with a call to be flexible and collaborative in the process of
experimentation.20 Here, as in Rose and Rabinow’s formulation of biopower, QS has
experts dealing with the vital character of living humans, but in a way that also makes
that authority accessible to any individual that wants to go through the process of
experimentation. This also limits that authority, however, and makes the revelations
about vital human characteristics applicable only to the individual giving the
presentation. The truth discourses of QS are ones that are understood as true as they
relate to the particular individual who found them although they are also presented as
possibly true for anyone else. The role of authority here is not to dictate a truth to be

119
followed, but to present a way of experimentation and working on the self that can be
tried by others and may or may not prove applicable.
By way of example, consider the case of Ben Finn: presenting at a London
Quantified Self Meetup Group, Finn described the process behind his attempt to
become an expert on his sleeping habits. For most of his life, he had trouble getting to
sleep, would constantly wake up at night, got up late, and was constantly tired during
the day.21 To fix these problems, Finn decided he would research potential solutions
through various medical websites and Google Scholar and then experiment on himself.
His goal here, as in all QS projects, is not to definitively figure out whether or not
certain sleep aides work for everyone or to find a normalized way of helping sleep that
works universally. Finn’s aim, instead, is to identify a personalized regime of care that
can help his sleeping habits. The audience members listening to the talk take these
conclusions as unique traits of Finn and a possible method of increasing sleep quality
that could be applied and tested on themselves.
His primary method of tracking was a phone app called SleepCycle22 paired
with paper and pen by his bed and an Excel spreadsheet. The app was installed on his
phone, which was then placed in his bed while he slept. By using the built-in
accelerometer, the phone was able to record how much Finn moved around in his
sleep and guess how much time he spent in different sleep cycles and create a sleep
quality number. Finn recorded this number, raw data from the app, and notes he took
when he would wake up in the middle of the night into an Excel document to see how
well he was sleeping.

120
From his Internet research, Finn identified 21 different factors that he could
test. These included when he ate dinner; whether he consumed alcohol, caffeine, hot
milk, a banana, or the chemical 5-HTP before going to sleep; whether he exposed
himself to orange or blue light; whether he had any distractions such as dawn light,
noise, a hot room, an unfamiliar room, stress, or illness; and whether he exercised,
meditated, or performed relaxation exercises before bed. All of these factors were
linked either by reputable medical studies or widely accepted belief to affect sleep
quality in normal individuals. However, these factors were identified through
experiments on large populations and affected a statistically significant portion of
individuals. For Finn, this did not mean that they would automatically affect his sleep,
but only that they were starting points. Expertise on Finn’s vital character of sleep
could not originate in large-scale studies, but had to be affirmed through self-
experimentation.
This re-orientation of who is able to acquire expertise on the individual body is
a drastic change in the way that biopower works. QS projects do begin with the
admission that medical knowledge has validity and truth to it. Population-based
studies and experiments are seen as useful information about bodies and medical
researchers are still labeled experts on vital character of the body. But, this vital
character is limited to a population that does not materialize within everyday life. The
body for QS projects exists as a part of a single individual that may or may not reflect
conclusions from studies on the normal population. The limits of institutional
biopower as something that only applies to non-lived, abstract populations begin form
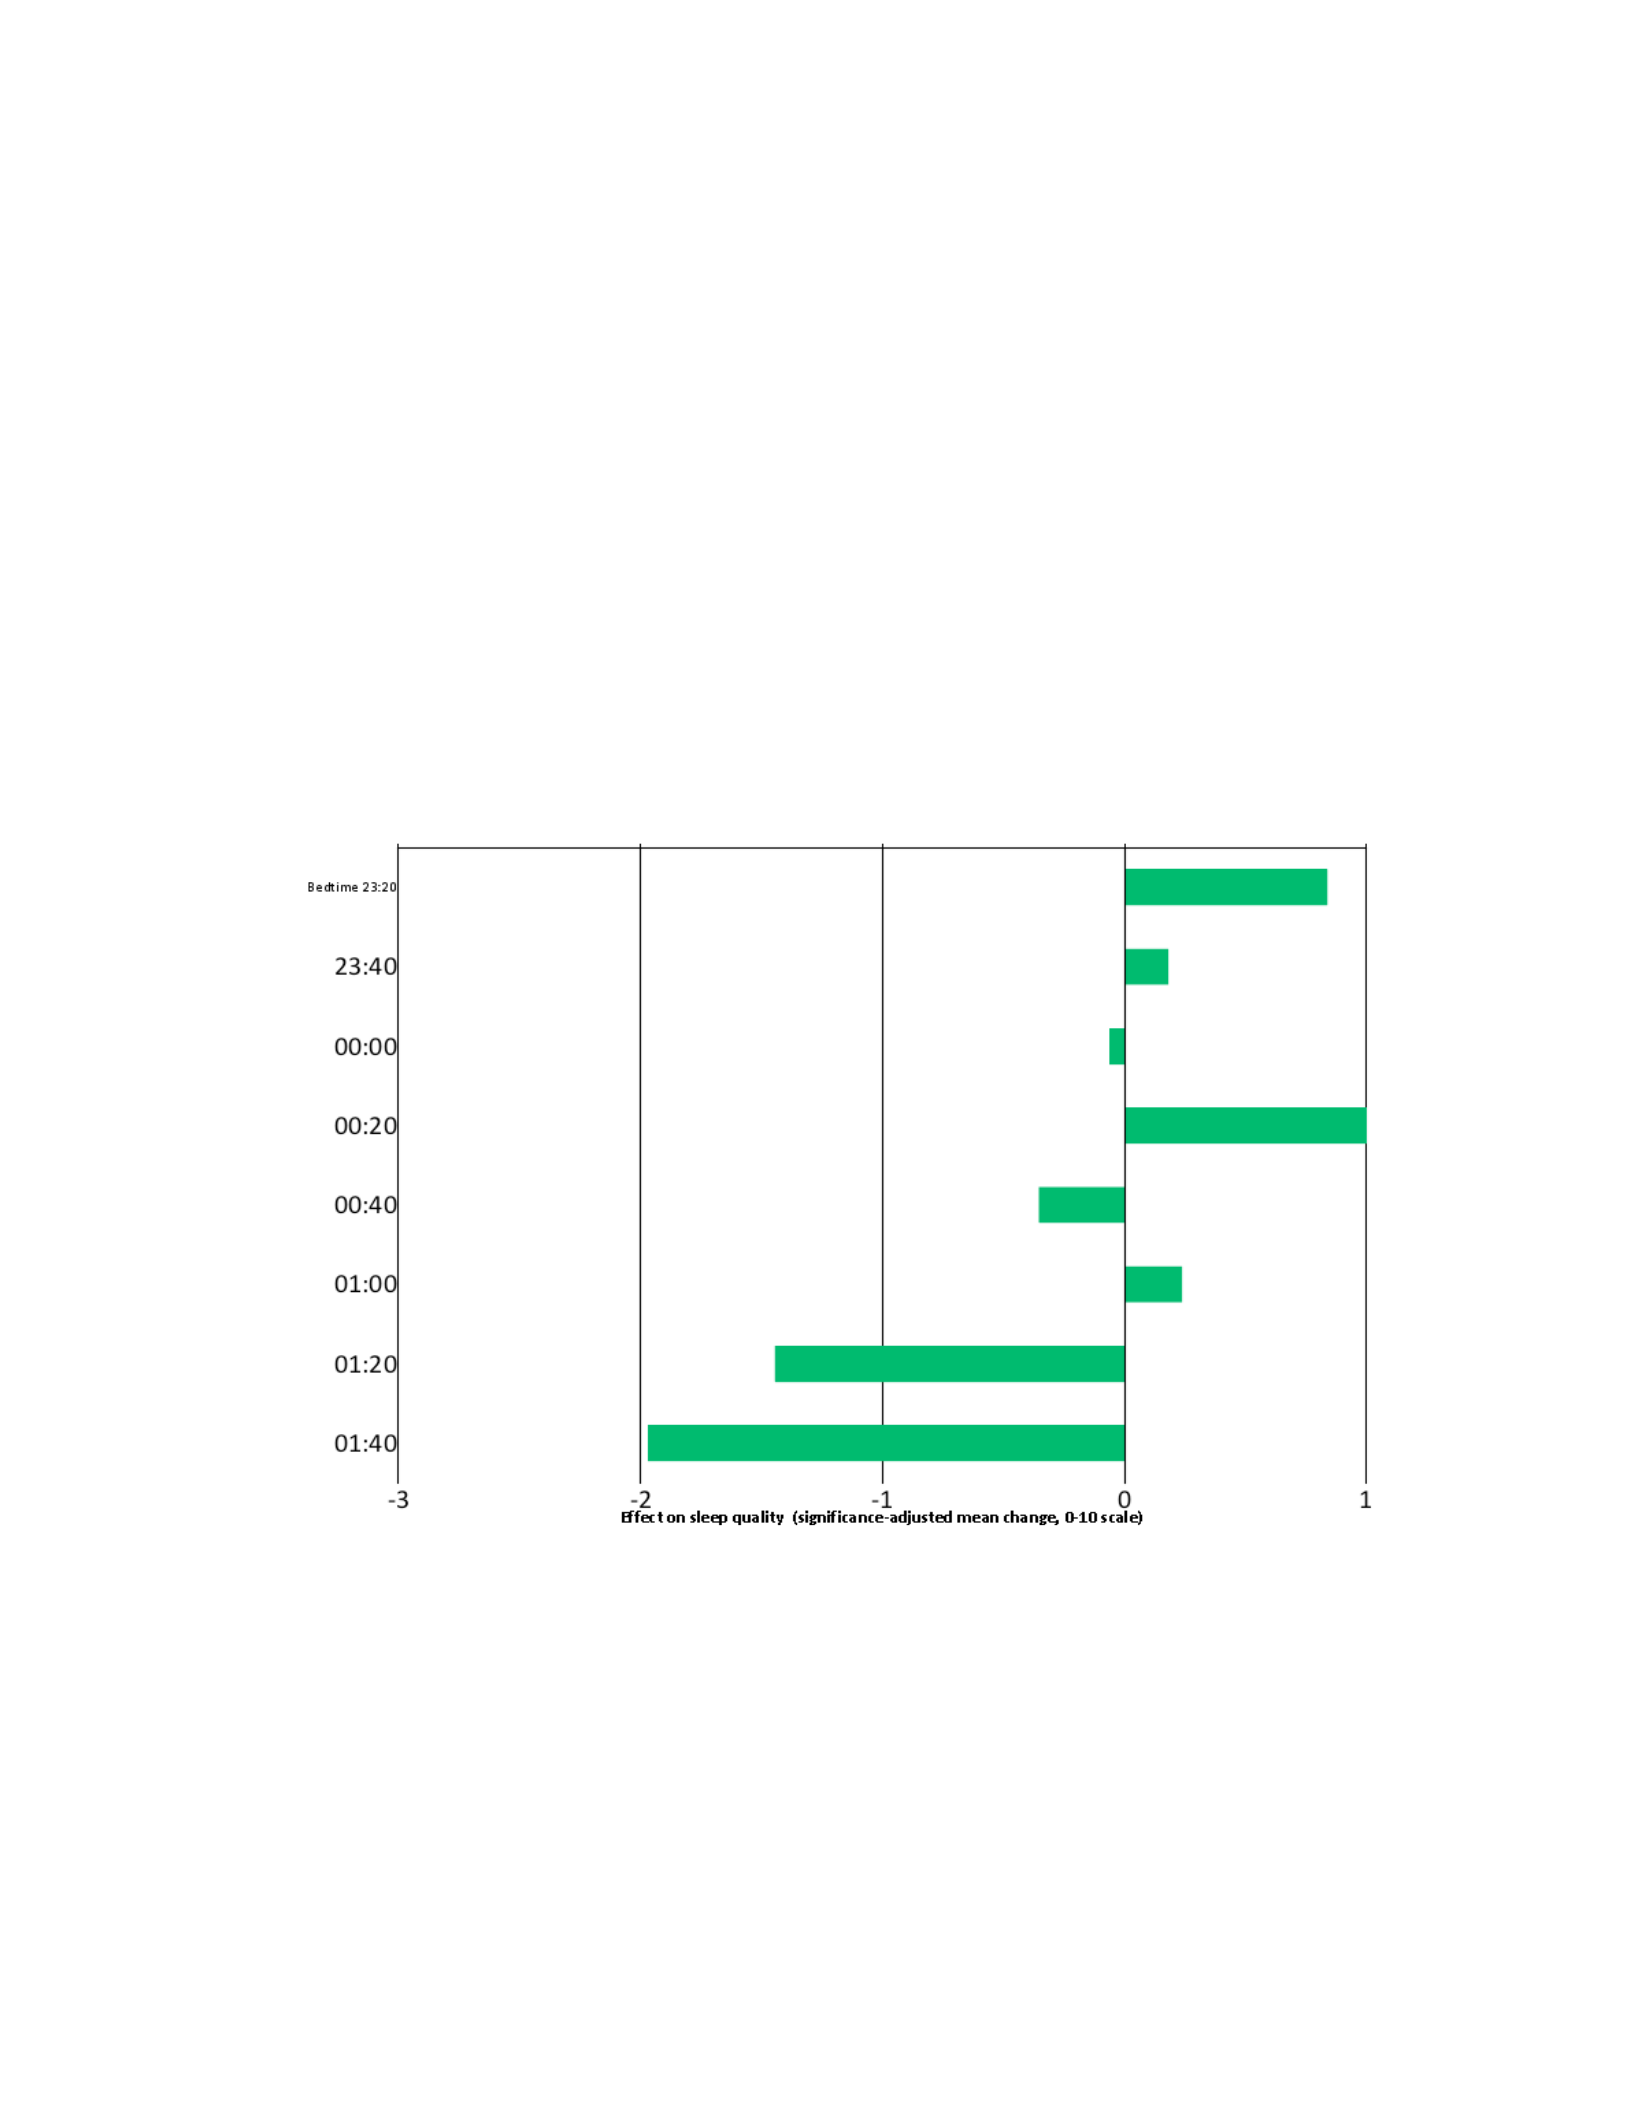
121
as QS projects see medical studies as truths, but truths that do not necessarily apply to
the lived, everyday body.
In order to create knowledge and truth about the individual body, QS projects
adopt biopower-based experimentation methods but apply them to single bodies, not
larger populations. For Finn, this means modifying the different factors he identified
over the period of 113 days and creating graphs of the data in relation to the resulting
sleep quality score. Consider two examples of these graphs:
Figure 3: Finn’s visualization of sleep quality
http://londonqs.github.io/qs/meetup-content/2014-10/qs-sleep.pptx
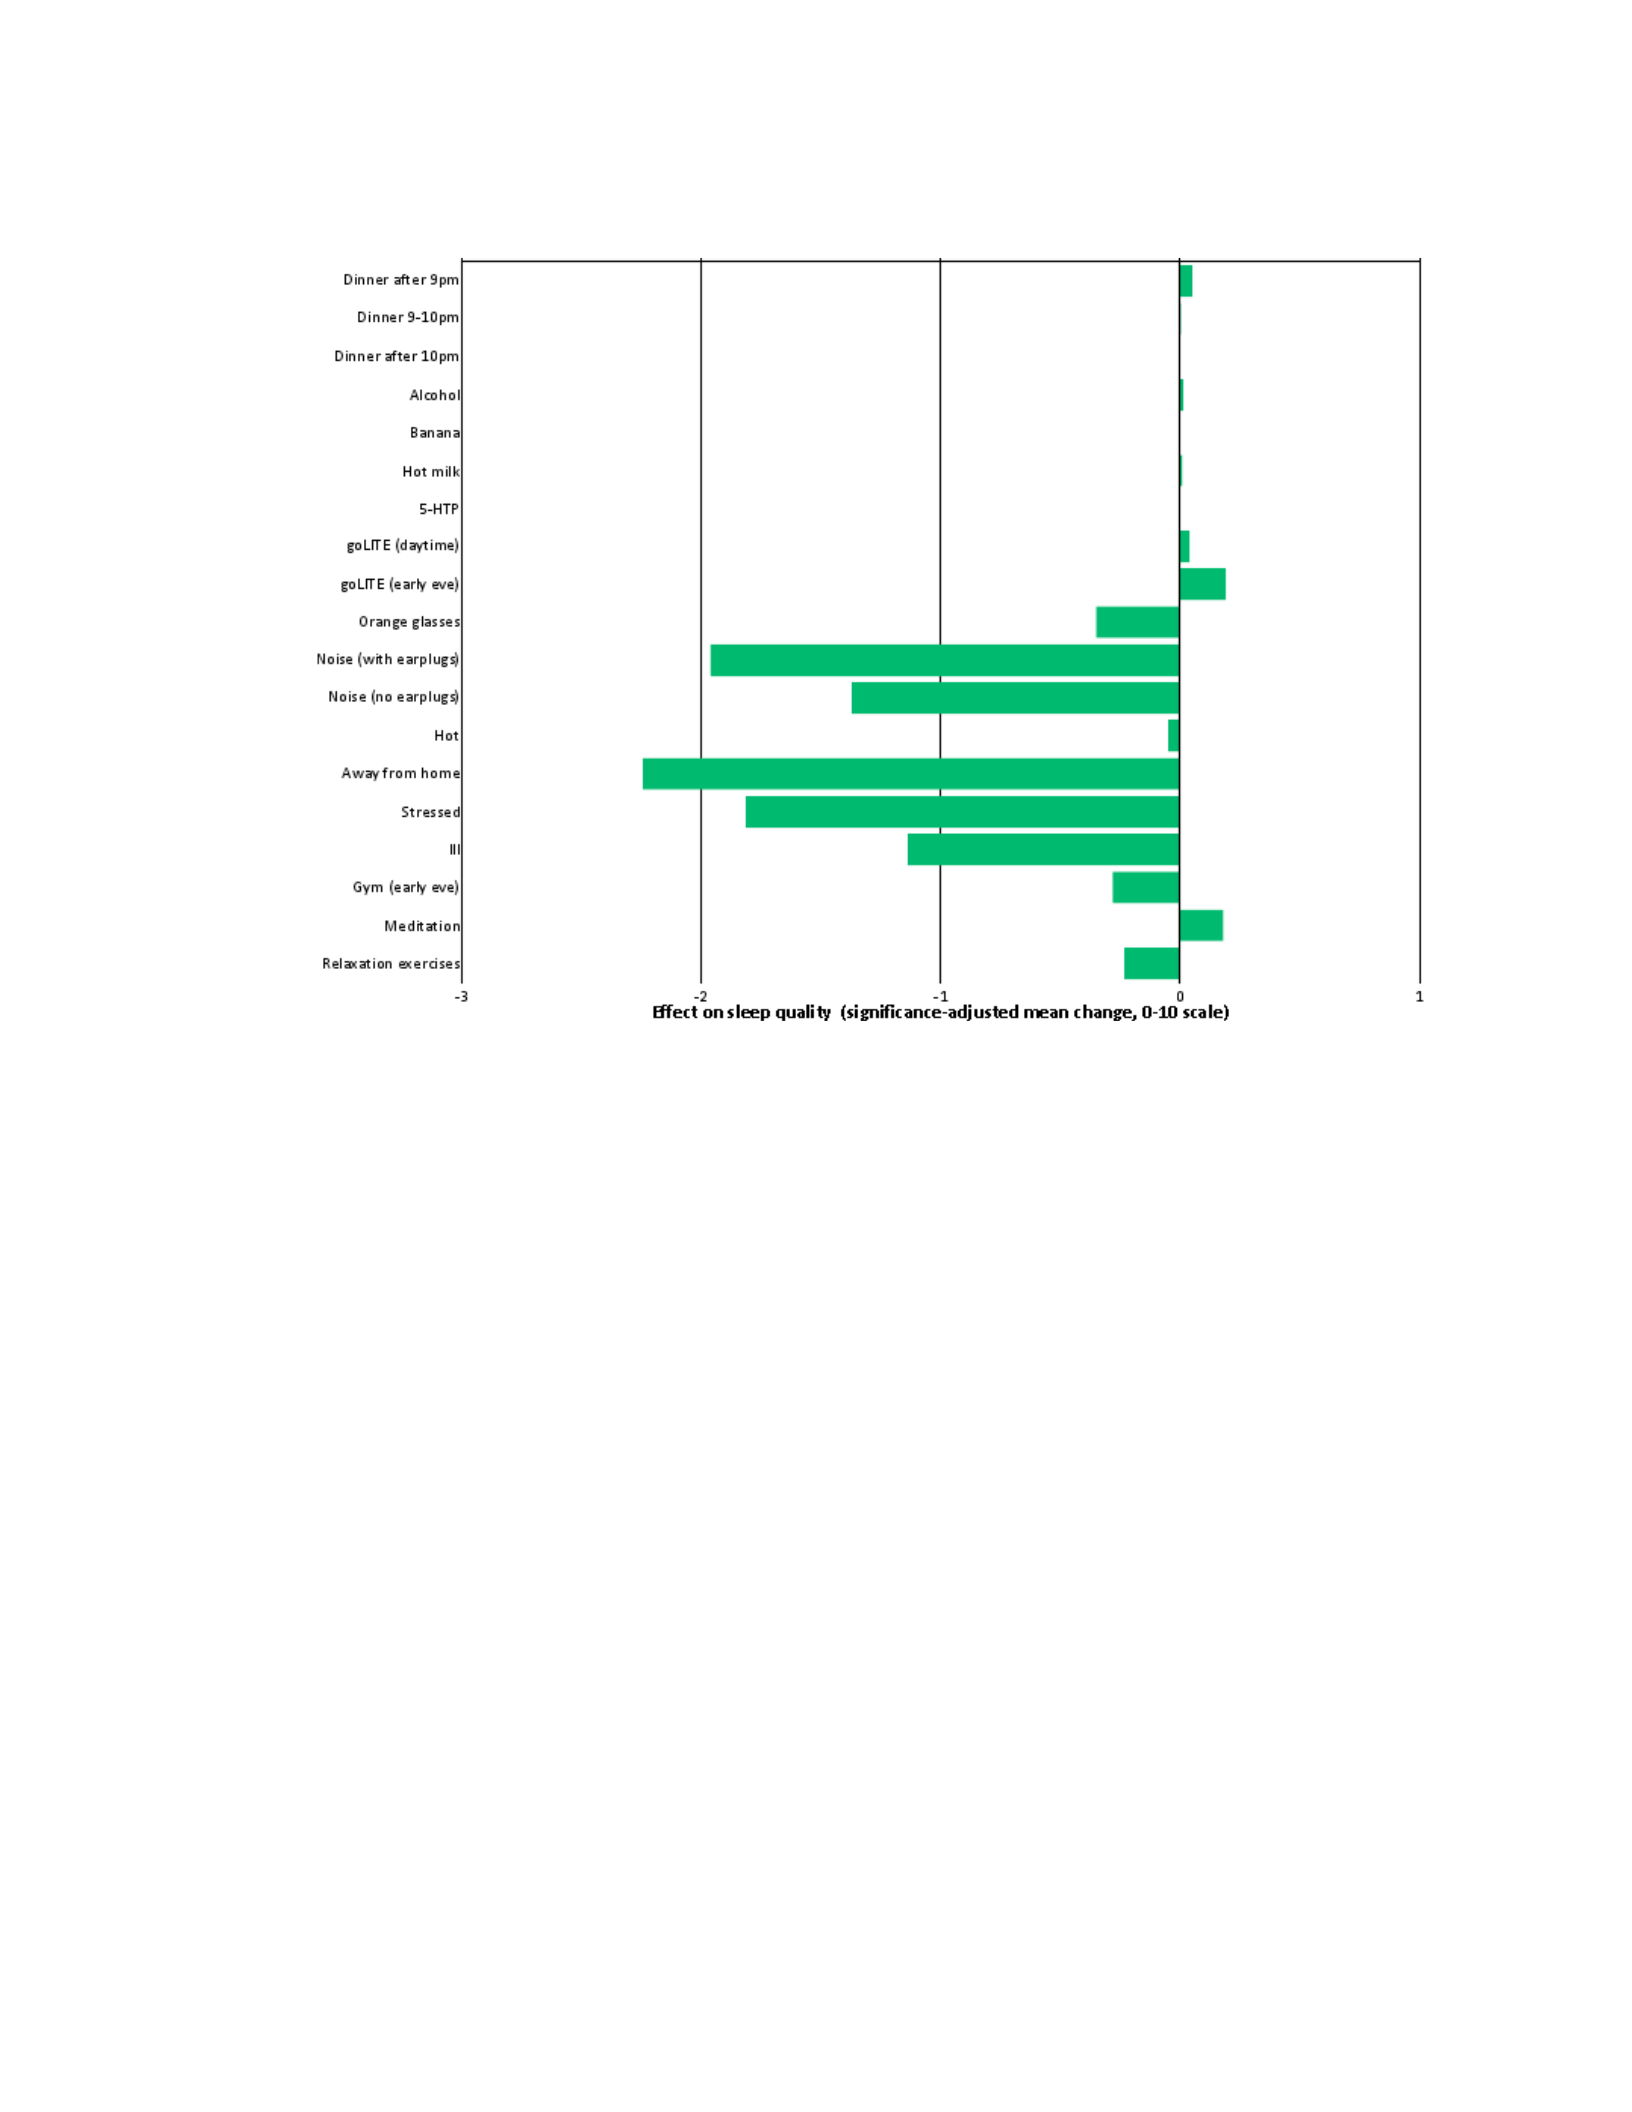
122
Figure 4: Finn’s visualization of sleep quality
http://londonqs.github.io/qs/meetup-content/2014-10/qs-sleep.pptx
The first graph shows the effect of different bedtimes on Finn’s sleep quality score.
There is no medically sanctioned optimal bedtime for a normal body and the sleep
score is a somewhat arbitrary number made up by SleepCycle, so Finn’s
experimentation here was not a comparison with pre-existing medical knowledge, but
used the metrics of sleep health in the creation of new knowledge loosely connected to
the medical field. He points out in his talk that he hoped to find a large spike that
would indicate a very obvious optimal time to go to sleep. However, the variation
between sleep times was minimal, effecting the sleep quality score by only about one
or two points in either direction. He observed that even so, the data more or less just

123
said that going to sleep slightly earlier was typically better, backing up what he calls a
more or less common sense conclusion.
The second graph is much more interesting. As with the first graph, it does not
show a large spike one way or the other in terms of a single factor that could help or
improve sleep. Nor does it show one factor that has an opposite of the intended effect.
Noise, stress, and unfamiliar sleeping situations all had negative effects, just as
medication had a slightly positive effect. What was significant about these results,
however, is that Finn’s sleep could only really be disrupted, not helped. A large
number of factors all would decrease his sleep quality while none presented a drastic
increase in quality. For Finn, this provided the knowledge that his sleep quality was
mostly improved by the subtractive process of minimizing distractions rather than the
additive process of incorporating new actions into his routine or aides like medicine.
Here, Finn came to a conclusion that does not necessarily go against medical
knowledge, as many of the negative influences of his sleep quality score are backed up
by scientific research and common sense, but manifests itself in a very particular way
by showing that some medically proven sleep aides do not work. As with traditional
biopower, it is possible to see a type of expertise on the body arise in Finn’s study, but
in a way whereby the expert has knowledge limited to a single body even as the
technologies used to create that knowledge remain very similar to those used in large-
scale biopower operations.
To continue his investigation into the vital character of his body through sleep
analysis, Finn also utilized a program called sleep.io23 to go through his sleep data and
124
recommend a change in sleep schedule to optimize his sleep. Initially, a graph of
Finn’s typical night of sleep looked like:
Figure 5: Finn’s visualization of his sleep stages
http://londonqs.github.io/qs/meetup-content/2014-10/qs-sleep.pptx
In this graph,* Finn’s time in a particular sleeps stage is represented by the blue bars,
with deeper sleep being a longer bar. He realized that he may have been sleeping for a
long time, but his sleep was fairly light. Sleep.io allowed him to recognize this pattern
and change his sleep schedule in order to condense it into less time, but deeper sleep.
After allowing for progressively less time to sleep, he trained his body to sleep in a
way that would create the following graph:
*
Note that this graph is a mock up from Finn’s presentation and not an actual graph. This explains the
odd time designations at the bottom. A true graph would most likely run from zero to eight at the
bottom.
125
Figure 6: Finn’s visualization of his sleep stages
http://londonqs.github.io/qs/meetup-content/2014-10/qs-sleep.pptx
Here, the total amount of time is decreased and the time in deep sleep is kept constant
or increased slightly. Finn was essentially able to remove the periods of restlessness
from the middle of his sleep cycle by allowing seven hours for sleep instead of the
typical eight. By sleeping less he was actually able to sleep better.
Though Finn does create his own conclusions and find ways that the vital
character of his body operates in ways different from what would be expected, he does
not stray too far from the technologies that produce relations of biopower. He
examines his body as a set of data that can be construed statistically, though these
statistics are for a single body over time rather than multiple bodies. Additionally,

126
many of the metrics that he uses go very much in line with traditional medical
knowledge. The importance of deep sleep, for example, comes from medical
knowledge and is not questioned by Finn. However, dismantling medical knowledge
as a whole is not the goal of Finn’s project or other QS projects. Rather, it is to apply
the technologies of biopower and the ways of creating knowledges about populations
in order to make them line up with everyday experience, which in this case is a single
body caught at the intersection of a variety of factors affecting sleep.
The second of the three aspects of Rose and Rabinow’s version of biopower is
that it must contain “strategies for intervention upon collective existence in the name
of life and health.”24 This underscores Foucault’s assertion that biopower works on
populations alongside disciplinary power. Disciplinary power served to work on the
individual body whereby institutions worked through interventions and regulatory
controls to enact “a biopolitics of the population.”25 By looking at large-scale studies
of a population’s health, biopower was able to create the idea of a “norm” that could
be enforced politically and socially to determine who could receive biopower’s ability
to foster life. These strategies were addressed toward different populations and
involve ways of defining forms of genetic or biological citizenship. Particularly
dangerous, these strategies often bring up categories of race, ethnicity, gender,
religion, etc. in order to enhance the condition of life of one group while dismissing
others.
For QS, this part of biopower slightly modifies Rose and Rabinow’s claim.
Many QS projects do focus on intervention in the name of life and health, but they do
not focus on collective existence in the same manner that traditional biopower does.

127
For example, Smarr’s project originated as a plan to lose weight and Finn’s project
was an attempt to live a healthier life through improved sleep. The bulk of the apps
and devices used by Quantified Selfers target health-base metrics that include: number
of steps in day (accelerometers like the FitBit, Basis, Mio, and others); sleep quality
(e.g. the now defunct Zeo, Sleep Cycle, and countless other iPhone apps); and calorie
consumption (e.g. MyFitnessPal or a simple spreadsheet). The one app created by
Quantified Self is a tool to export data from Apple’s HealthKit health data aggregator
into a “a simply-formatted table so that you can make health, fitness, and other
discoveries by exploring your own data.”26 The data that this app exports is
exclusively health-related: daily/hourly reports on active calories; blood alcohol
content; blood glucose levels; diastolic and systolic blood pressure; body fat
percentage; body mass index; body temperature; caffeine consumption; cholesterol;
cycling distance; electrodermal activity; flights of stairs climbed; heart rate; inhaler
usage; lean body mass; number of times fallen; oxygen saturation; respiratory rate;
weight; and consumption of a number of vitamins, minerals, and macronutrients.27
Also along the lines of Rose and Rabinow’s formulation of biopower, the QS app
makes the data available to users so that they can tinker with the data and create
“discoveries” about their health data which can then be used as the basis of a plan for
changing or modifying aspects of life and health for the individual. Looking at QS in
terms of biopower allows us to see these moves as techniques of governmentality and
population control that are being re-appropriated by individuals and used to create

128
subjects that are unique iterations of the “normal” subject produced by institutional
medicine.
Even as the sentiment behind QS is to do work on the life and health of a body,
as in biopower, it strays from the traditional formulation of biopower because it does
not act on populations at large, but on a single body. The n=1 slogan of QS proves to
be extremely significant in this regard: it demonstrates the QS idea that the individual
can be converted to a dataset, but significant in its own right and not necessarily as a
single part of a population. In Smarr’s case, for example, he did not compare his food
intake and movement to what should be healthy for the general population. Instead, he
took his overall food intake and movement as its own dataset with its own ideal
“healthy” range. Likewise, Finn examined his own sleep patterns as a function of a
single body over time, not in relation to a larger population. In the n=1 mentality of
QS, biopower’s effect on “collective existence” means not the collection of multiple
bodies spread out over space and time, but tracking a single body as it moves through
time to understand aspects of life and health.
Katie McCurdy is an example of how tracking information about a single body
can be used for health-related interventions. She makes the claim that even though
some people may self-track from a sense of narcissism or vanity, one of the major
reasons for self-tracking is “medical necessity.28” By this, she means the need to
maintain oversight on chronic conditions so that medically-sanctioned changes can be
introduced into a person’s lifestyle to allow them to continue to live healthily. Such a
process is very similar to Rose and Rabinow’s claim that biopower works through
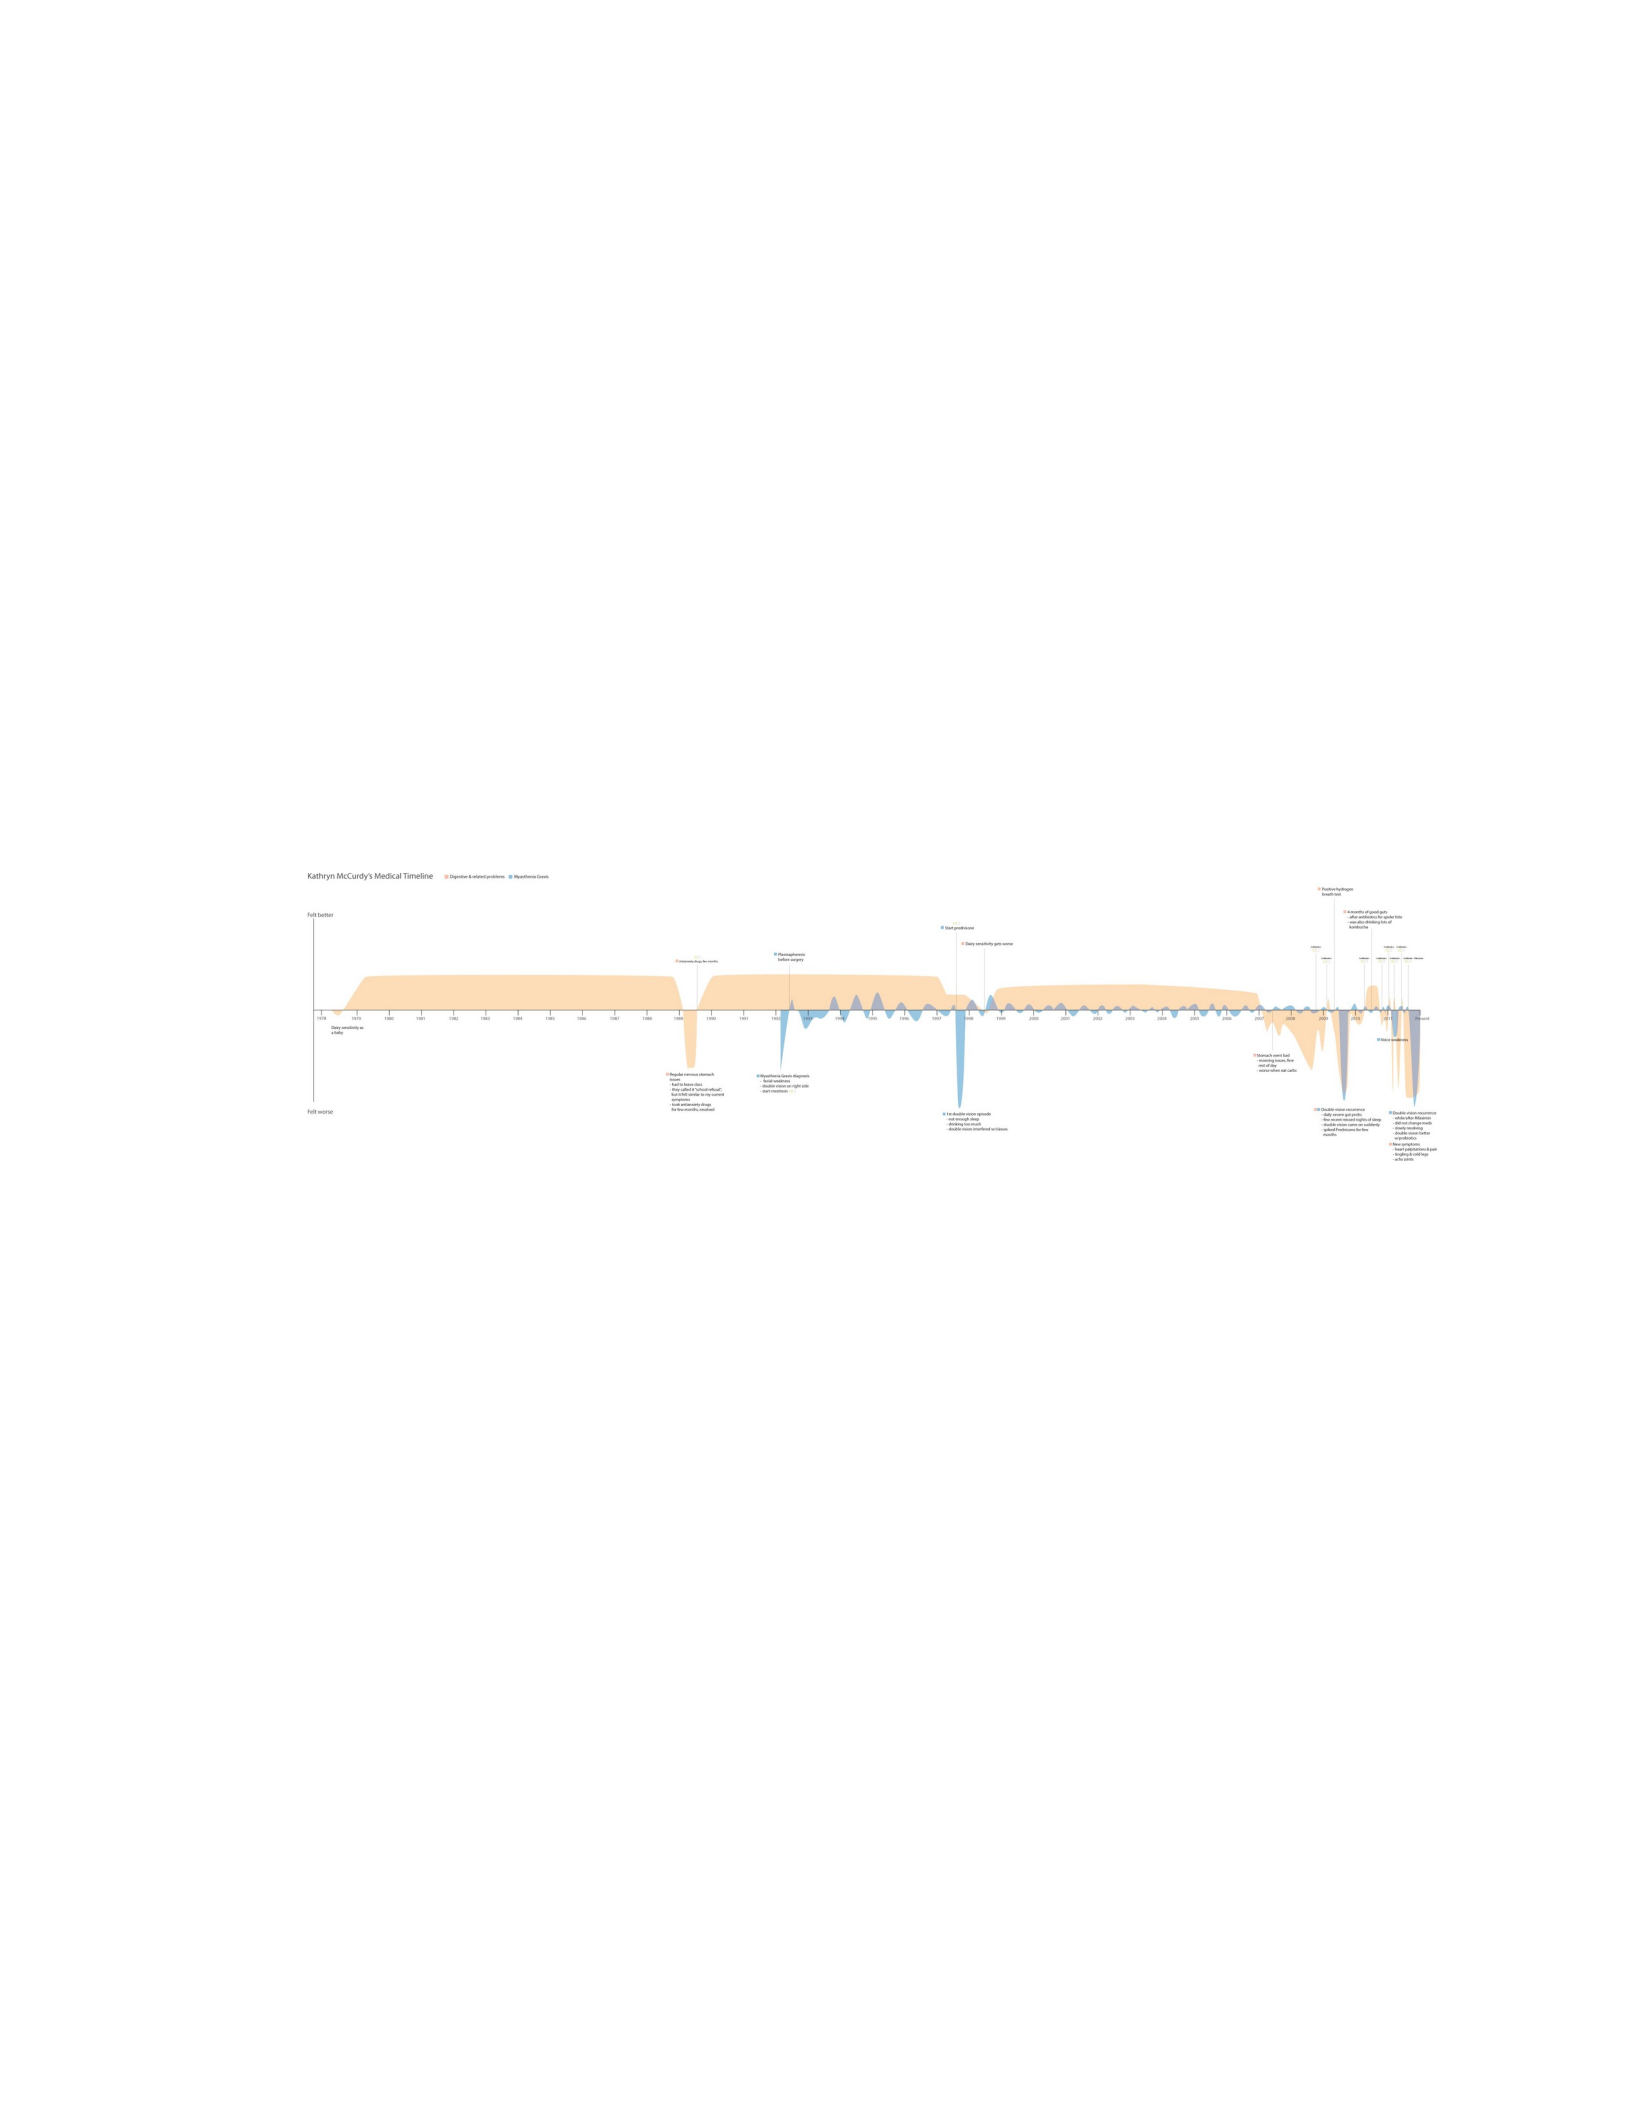
129
creating strategies for intervention on collective health and life. But, again, in the case
of McCurdy and other QSers, these strategies operate on the individual level and not
the level of the general population.
McCurdy has an autoimmune condition called Myasthenia Gravis, which
causes weakness in voluntary muscles.29 In order to better communicate with her
health care providers, she created a data visualization that included developments in
her autoimmune disease, gastrointestinal issues, when she started or stopped certain
medications or made any dietary changes. A selection of this data visualization looks
like this:
Figure 7: McCurdy’s visualization of Myasthenia Gravis flare ups
http://quantifiedself.com/wp-content/uploads/2012/03/KM_med-timeline.png
The aim of these visualizations was twofold. McCurdy wanted to create an overall
picture that could tell a story about her past health to her doctors and was more
accurate than the “blurry picture” typically provided through forms and quick
interviews with patients.30 She also wanted to demonstrate to her doctor a connection
between gastrointestinal issues and Myasthenia Gravis flare-ups that couldn’t be
explained by existing medical models but had occurred for McCurdy since she was
13.31

130
What is interesting about McCurdy’s process is that medical knowledge retains
a privileged place as the source of what the interventions on health should be while the
data that gives rise to the assessment comes from the actions of the patient. In her
words: “The patient is providing contextual information about his or her OWN
situation that compliments the doctor’s past experience, expertise, and test results,” a
move that gives precedence to medical knowledge as a way of providing guidance for
self-care while making the individual the basis for judgments about that guidance. The
technologies of biopower – expert medical knowledge and a focus on ordering the life
of the patient – do not disappear and the power dynamic is not simply reversed by the
patient directing their own care. McCurdy’s case acknowledges medical knowledge as
legitimate and necessary for “healthy” life, but also assesses that knowledge according
to an individual case. The goal of medicine’s intervention into McCurdy’s practices of
self-care is not to bring her in line with what a “normal” human would be, but to
anticipate and deal with issues that arise as she lives with her disease. Much as with
Finn’s case, the “normal” human that McCurdy uses as a basis for comparison of her
own state is the image of herself created over time. Through visualizations and graphs,
she is able to understand how she reacts to certain drugs and how her symptoms are
interrelated, providing a basis for a plan to intervene on various aspects of her health.
For Rose and Rabinow, biopower’s operations on the life and health of
populations expands to create “biosocial collectivities” such as “race, ethnicity, gender
or religion, as in the emerging forms of genetic or biological citizenship.”32 By this,
Rose and Rabinow mean that the techniques of biopower attempt to modify the life

131
and health of populations in such a way that certain individuals both identify and are
identified with a particular community or nation while others are excluded. The
principles of exclusion here are based on how well an individual lines up to a pre-
determined concept of what is “healthy”; those that are deemed “unhealthy” are either
excluded from the community or forced to re-configure themselves to fit that idea. In
cases like McCurdy’s, these principles of exclusion are not put into play exactly as
Rose and Rabinow conceive it. On the one hand, medical knowledge is the originator
of many concepts of what processes of self care are healthy or sufficient to support
life. McCurdy still brings her data to a doctor, who then interprets it and prescribes
different treatments. Through these treatments, she is able to decrease the expression
of her symptoms and fall more in line with a typical level of health for an individual in
her larger social and national context.
This would seem to place responsibility back on the individual to adhere
toward larger notions of health by self-tracking. Yet, McCurdy does not take over all
of the tasks usually attributed to the medical institutions. She collects a large amount
of data, organizes it, and makes assessments, but still relies on conversations with a
doctor to make final judgments. By creating an archive of individual data and an
initial interpretation, she performs an important task that changes the scale at which
biopower operates. By tying any medical analysis to a set of data from a single
individual, McCurdy does not allow the resulting conclusions to become an accurate
baseline for the “normal” healthy state of any individual. Any assumptions about her
health conditions or how to treat them are limited solely to her individual instance. In

132
this way, biopower inserts itself into the life of McCurdy, but does not expand to
create a biosocial collectivity determined by institutional medical knowledge.
The third characterization of biopower brought up by Rose and Rabinow
foregrounds the ways in which individuals engage in “modes of subjectification” or
“work on themselves, under certain forms of authority, in relation truth discourses, by
means of practices of the self, in the name of their own life or health, that of their
family or some other collectivity, or indeed in the name of the life or health of the
population as a whole.”33 Just as Rose and Rabinow’s second point spoke to the way
that large-scale institutions intervened into the lives of individuals and created
collectives based on a certain expression of health and life, their third observation
about how biopower works speaks to the ways that individuals internalize certain
discourses to intentionally line up with certain institutional expectations of how they
should order their lives.
The examples of Smarr, Finn, McCurdy, and other QSers seem to fall in line
with this aspect of biopower. Each of these individuals took it upon themselves to
create a regime of self-care to change certain aspects of their life in order to be
healthier. Smarr tried to lose weight and also to pre-empt the onset of his Crohn’s
disease. Finn found a list of actions to avoid in order to sleep better and trained his
body to sleep more efficiently in less time. McCurdy used her data to organize her life
in a way that lessened her Myasthenia Gravis symptoms in ways sanctioned by a
medical professional. In each case, the QSer works on themselves in the name of
health according to a form of authority or in relation to a truth discourse. Significantly,

133
however, these authorities and truth discourses do not arise from institutions, as in the
traditional formulation of biopower. They first originate in the individual and are then
filtered through medical knowledge. Applications of biopower are always a navigation
between individuals and institutions, but in the case of QS projects, the individual
becomes the arbiter of what type of knowledge justifies a certain type of intervention.
As QS projects allow self-care procedures to be assembled by the individual
instead of the medical institution, the justification also becomes slippery. Medical
knowledges, as shown in the previous chapter, seek to work on the abstract level,
creating a generalizable body of knowledge about a disease that de-individuates
circumstances. As the analysis of biopower shows, this body of knowledge then
becomes the basis for a justification for administering life through regimes of self-
care. But in QS projects, this justification does not become fixed; it constantly
changes through time, depending on the individual’s unique circumstances. As a
result, the focus is not on building a large archive of knowledge about medical
conditions that can then be utilized in processes of marking entities as normal or
abnormal, but on the process of self-care itself.
Nancy Daugherty’s QS project demonstrates this tendency. Daugherty initially
began to use devices such as the FitBit and Aria solely to record her movements and
weight in order to learn from them, much like Smarr. She did want to lose weight
through the technology, but her primary goal was to track herself just for the sake of
tracking. She initially expected the technology to present data to her that would tell
her what needed to be changed, as traditional medical knowledge would diagnose a

134
disease and recommend a treatment. However, this turned out to be, as she states, a
“miserable failure” because she would be very dedicated to tracking a particular
aspect of her life for a few weeks and then would become bound up in a stressful
situation and forget to continue recording what she set out to track. She was left with a
“wasteland of empty biometric profiles,” aside from a year’s worth of data about her
weight. Her data was incomplete by any sort of rigorous scientific standards and
would not be able to give her any sort of definitive answer on how to reach her goal,
like the QSers mentioned above. By looking at a graph of what weight data she did
have, however, she found that it correlated directly with her emotions. Stress at work
or in her personal life made her weight go up while her tracking went down, and less
stressful periods or instances when she had more time to exercise caused her weight to
go down at the same time her tracking increased. Oddly enough, even with
Daugherty’s inability to fully integrate the technology into her body or life, the gaps in
tracking provided by the technology still created a compelling and instructive picture
of her self. This was not an incomplete or partial set of data after all, but a set of data
that showed a different picture than she expected to find.
After identifying the connection between weight and tracking, Dougherty then
began to track her emotions in an organized manner along with the biometric data that
accompanied them. She would find when she had the most energy during the day,
when she felt happy or sad, and biometric data like movement, sleep, and heart rate.
The most significant thing that Dougherty found did not come from the data itself, but
from her reaction to the actual process of tracking. She points out that the more she

135
tracked, the less the data meant to her because “just by tracking [her] emotions, [she]
was completely changing them.”34 By paying more attention to what her emotions
were at any given moment, Dougherty found that she could manage them better,
creating more positive ones and avoiding or countering negative ones. To help her pay
more attention to her emotions at any given moment, Dougherty created a string of
LED lights connected to a sensor that could tell when she was smiling. Her device
would record when she smiled and it would give her immediate feedback through the
blinking lights so that she could then bring her attention to how she was feeling. The
sensor would also give feedback to tell her when she had not smiled in a while,
blinking to encourage her to engage in a positive emotion. For Daugherty, “self
knowledge through numbers” did not just mean knowledge emerging through static
numeric data sets, but knowledge emerging from the creation of those numbers.
For Daugherty, the data and the self she formed through that data was less
important than the introspection provided by the process of self-monitoring. Picking
up a term used by other QSers and Buddhist tradition, Dougherty calls this
“mindfulness,” a process she describes as “observing inward” and “the act of
observing ourselves with openness, curiosity, and acceptance.”35 Mindfulness is, in
QS, “regulating your attention to the moment, observing without judgment.”* In her
*
Ramirez, Ernesto. QS and Mindfulness Quantified Self. quantifiedself.com. Web. 28 Feb. 2013.
<http://quantifiedself.com/2013/02/qs-and-mindfulness/>. There is an interesting connection here with
Husserl’s concept of the phenomenological reduction, which is a way of looking at the world without
preconceived or socially-constructed judgements. In both cases, the subject enters into a certain frame
of mind that does not take anything for granted and attempts to bring out how we interact with the
world in ways that we may not otherwise be aware of. In this sense, the QS process is much like
phenomenology put into everyday practice. For more on the phenomenological reduction see Husserl’s
Ideas II.

136
project, her main goal ended up being an attempt to better herself through controlling
her emotions, but in order to do that she had to make herself aware of an aspect of
herself, namely how she interacted emotionally with environments and individuals. It
was not the technology itself that performed this task through raw data, but rather
facilitated Dougherty’s introspection and attention to her emotions by allowing her to
look at her self in a particular way. As she notes, this introspection actually became a
habit through her use of technology to the point where the data just provided
verification of what she was doing rather than a basis for action in and of itself.
Daugherty’s project falls very much in line with Rose and Rabinow’s third
observation about biopower. The actual act of tracking and the introspection that
results is largely the point of her project, creating a practice of the self where she
attempts to make changes in her habits and way of life in the name of health. This case
is unique in relation to biopower because it still acts under certain forms of authority
and truth discourses, but they do not stem solely from the medico-administrative
complex as in the more traditional model of biopower. By collecting her own,
somewhat incomplete data, Daugherty is able to become an authority on herself and
the workings of her body. The conclusions that she draws – namely that paying
attention to her emotional state positively effects her mental health and weight – are
ones that do not necessarily go against medical knowledge but do not derive from
sanctioned medical studies. Like McCurdy and Finn, Daugherty’s project utilizes the
technologies of biopower but forms knowledge outside of the medico-administrative
institution.

137
For Rose, the application of biopower becomes a political discourse of risk
avoidance, where the state and medical institutions argue that we should minimize
harm to our bodies in order to avoid economic effects on the economy, such as days
of work lost to sickness or increased insurance costs for everyone.36 To an extent, QS
fits into this model as projects are largely focused on boosting physical and mental
health. However, the discourse around many of these projects center around
increasing personal health for its own sake or for the benefit of the individual
themself. Smarr, Finn, and McCurdy all used QS principles and biopower
technologies to become healthier individuals, but their primary motivation was not to
live up to society’s expectations of them or become more efficient solely to produce
more capital. Smarr and McCurdy were attempting to get a medical condition under
control so they could live comfortable lives and Finn was trying to minimize sleep
issues that were affecting his own well-being. In each of these presentations, work
was not a primary concern for the QSers.*
By removing work as a motivator, the discourse surrounding QS projects
becomes one of introspection and self-knowledge. Daugherty, for example, began her
project trying to lose weight but then ended up creating a process whereby she
attracted attention to her own emotional state through her process of “mindfulness.”
The end goal of her project is greater knowledge of her self and how she works within
certain social contexts so that she can be “happier.” While the individuals who
engaged in these projects thus far all had a distinct goal in mind when they began their
*
See chapter four and the conclusion for a more detailed examination into how health tracking

138
tracking, many QS projects track for its own sake. As Daugherty pointed out in her
presentation, the act of tracking has the ability to focus attention on the processes of
self-care and aspects of the individual that would otherwise be hidden. Unlike
traditional biopower, the biopower found in QS projects has personal exploration as its
primary goal.
If the projects thus far considered all highlight the importance of personal
health and development however defined, Stephen Wolfram’s project is one of the
best examples of tracking and self-monitoring for its own sake. Though he is not
explicitly aligned with QS, Wolfram calls his tracking “personal analytics” and
utilizes many of the techniques that QS projects use and could be said to be a
precursor to the movement. As a pioneer in computer use, programming, and
technology, Wolfram began tracking various aspects of his life from early on. Starting
around 1989, he tracked his email usage and then began to also record keystrokes,
phone calls, steps, and calendar events.37 For years, he did very little with this data,
aside from having an automated program email him reminders about what happened
the previous day. In 2012 he finally began to sift through the data and see what sort of
information about himself he could garner from it. That means that for about 23 years,
Wolfram collected data about his work habits and his productivity but did not use it
for any specific purpose.
technologies figure into labor and risk.
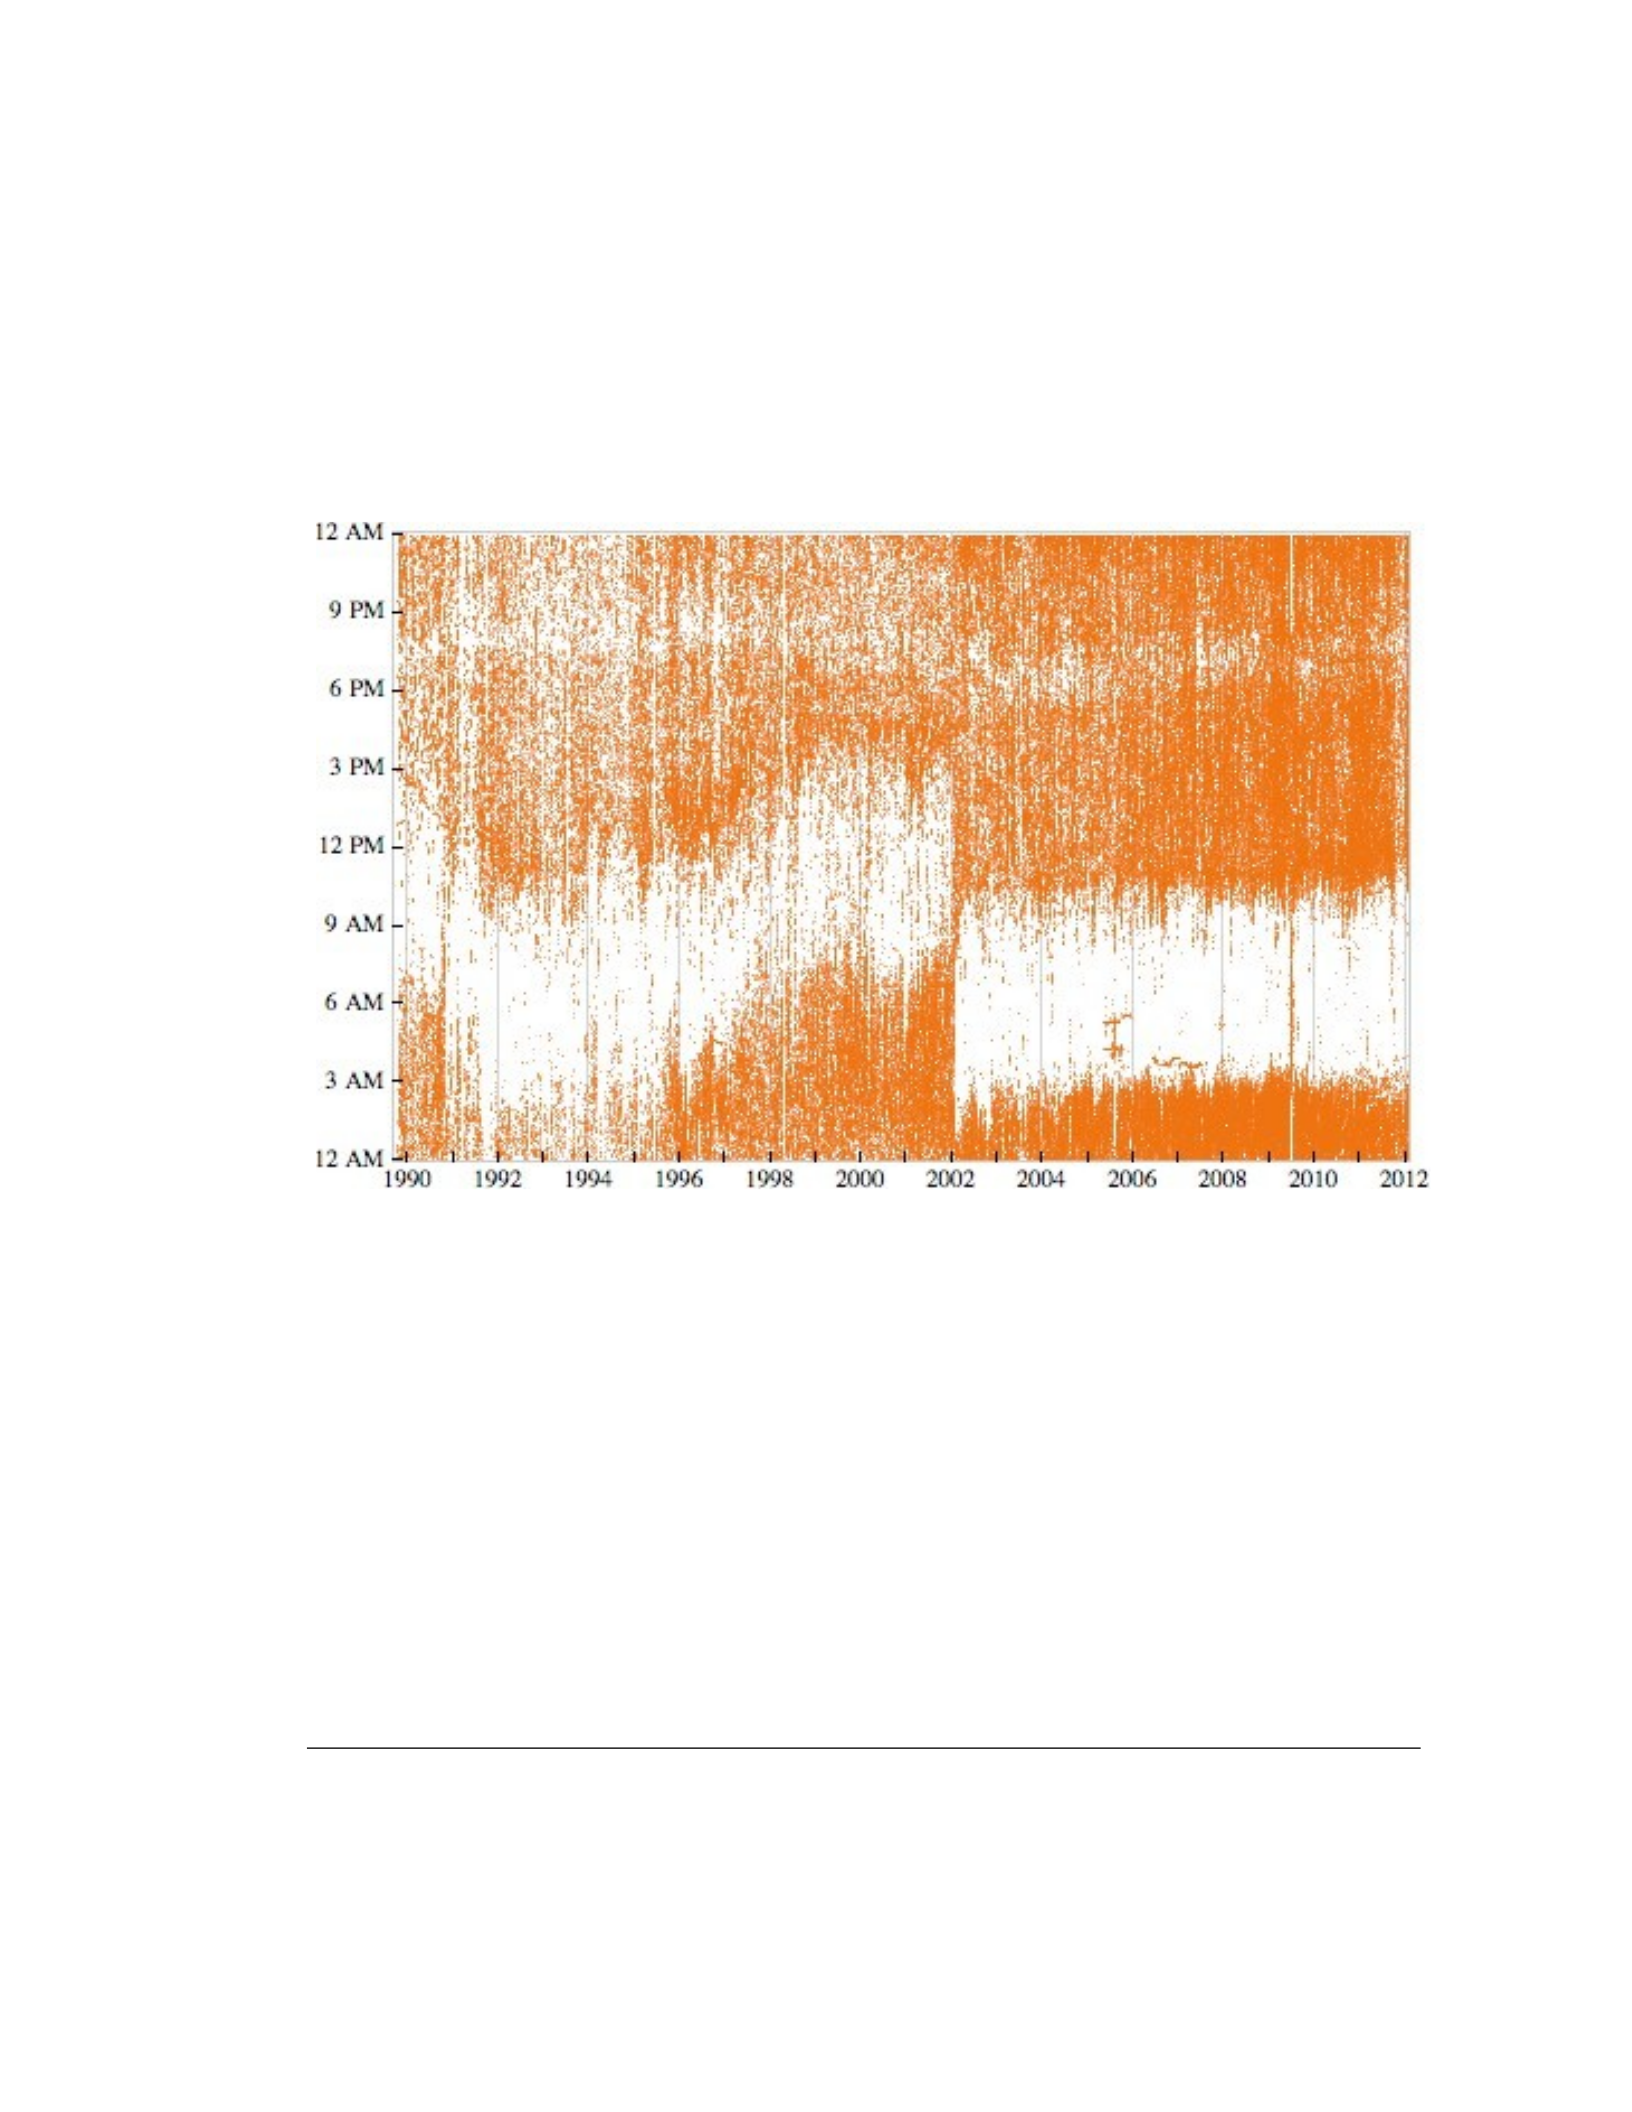
139
Wolfram began by running the data through an analysis on Wolfram|Alpha
Pro.* This program sorted through all of the different variables and allowed Wolfram
to output a number of different types of graphs. Some of these graphs plotted the
number of emails alongside the time of day they were sent:
Figure 8: Wolfram’s visualization of email volume
http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life
Others plotted the daily volume of emails:
*
Stephen Wolfram Blog : The Personal Analytics of My Life. blog.stephenwolfram.com. Web. 5 Feb.
2013. <http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life/>.
140
Figure 9: Wolfram’s visualization of email volume
http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life
And still others showed the number of different recipients:
Figure 10: Wolfram’s visualization of email volume
http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life
Unlike typical science experiments, Wolfram had no hypothesis when he was
collecting this data, nor did he come up with one as he was creating the graphs. These
graphs were all generated in order to see if there was anything interesting or
significant in the aspects of his life that he could track. Wolfram used this data as a
way to create a vision of himself that had been filtered through a software program
and could be held up and interrogated. The email tracking programs had their own
particular intentionalities that allowed Wolfram to look at himself in terms of time and
email – something that would not be possible for him without the software designed to
141
reveal it. This is not meant to be a complete picture of who Wolfram is or what he
does, but it allows for a particular aspect of himself to emerge that comes from the
data and from the intentionalities of the technology used to gather it.
The data in the above graphs draw a picture of Wolfram as a very constant
individual with an increasing need to use email, but it also serves as a record of
important life events. The first graph shows a gap in email usage between 6am and
12pm from 1990 to 2002. In 2002, there is a dramatic change where Wolfram tends to
no longer send emails from 3am to 9am. In the 1990’s, Wolfram was working on a
book and restricted his work to the nighttime to minimize distractions. Here the data
does not necessarily contradict or open up any new insights into Wolfram as a person,
but reinforces knowledge of habits that he already had. The data and the graphs do,
however, present a portrait of Wolfram through the lens of email-tracking technology.
Wolfram’s calendar data shows a similar story. He plotted the number of
events based on time of day over the course of years:
Figure 11: Wolfram’s visualization of events
http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life
As would be expected, when he was working nocturnally on his book Wolfram had
few events. After 2003, Wolfram’s reintroduction into the daytime world and
142
increasing sociality becomes evident in the graph. He becomes busier, but still is
remarkably consistent in having few events in the morning and nighttime as well as
having an event-free family dinner time slot around 6-8pm. Like the email data, this
graph does not show any revelations about Wolfram or his working habits, but serves
as a record of a particular aspect of himself that he can divorce himself from and
examine.
After creating dozens of graphs and looking at alternative ways of sorting
through the data, Wolfram compiled a comparison graph of all of his information:
Figure 12: Wolfram’s visualization of email data alongside events
http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life

143
His analysis of the data, again, does not relay any surprise, but is still reassuring:
The overall pattern is fairly clear. It’s meetings and collaborative work
during the day, a dinner-time break, more meetings and collaborative
work, and then in the later evening more work on my own. I have to
say that looking at all this data I am struck by how shockingly regular
many aspects of it are. But in general I am happy to see it. For my
consistent experience has been that the more routine I can make the
basic practical aspects of my life, the more I am able to be energetic—
and spontaneous—about intellectual and other things.38
Wolfram’s personal analytics project becomes not a way of making a distinct change,
but reflects a part of the QS process whereby the data becomes the basis upon which
questions are generated. Wolfram’s project involved collecting data for its own sake,
rather than in the service of a particular project. Moreover, the act of tracking allowed
him to visualize routine and habits that he was already engaging in. This is significant
because Wolfram did not use the tracking software to help integrate specific habits or
behaviors into his own life in the way that biopower seeks to organize daily life by
providing standards and guidelines for healthy living. Instead, Wolfram was able to
create a concept of what his life looked like from the data, which could then be
extrapolated into what a “healthy” or “unhealthy” life might look like. In this case,
Wolfram showed graphically how he spent his time when he finished his book,
providing an example of successful project management that could be used in his own
future projects or as a blueprint for other people to follow. Or, for example, if
Wolfram became sick or depressed, he could attempt to map it onto a graph of how
his working hours had changed at the beginning of the sickness, exploring one
possibility for the origin of the sickness.

144
On the one hand, QS projects could be seen as a way to identify and remove
the hidden operations of institutional biopower. By collecting large data and showing
emerging patterns (as Wolfram does, for example), it could be possible to find ways
that individuals have unintentionally ordered their lives according to perceived healthy
or unhealthy habits. Many QSers seem to do this. Smarr, Finn and Daugherty all used
self-tracking to see how their lives were being adversely affected by certain habits that
they could see the effects of, even though they could not identify the case. Smarr and
Daugherty each attempted to find what poor habits were causing them to gain weight.
Finn tried to identify factors that were causing him to lose sleep. In each of these
cases, identifying the offending causes of health issues also draws a line around the
limits of biopower. The QSers are able to find out what authoritative health-related
suggestions they are implementing in their daily life and how successful each of these
are. Potentially, this would allow for individuals to create a body of knowledge that
undercuts the authority of medico-administrative knowledge by allowing for health-
related knowledge that applies only on the individual level and sometimes explicitly
goes against proven medical guidelines. Finn would be a prime example of this, as he
found that many of the typical suggestions for fixing sleep issues didn’t work for him.
However, this conclusion would fail to acknowledge that Quantified Self
projects themselves represent an expansion of biopower and still often work in tandem
with population-based health studies. As demonstrated above, many QS projects
follow Rose and Rabinow’s formulation of biopower, encouraging individuals to
work on themselves in the name of health and perpetuating the role of the “expert,”
even as
145
its influence is diminished. Moreover, the heavy emphasis on presenting projects to
others as possible solutions for their own problems, opening up data sets for others to
experiment on, and Big Data-style data logging all retain the necessity of an
institutional component. Quantified Self then appears to be more of a reconfiguration
of institutional biopower rather than a complete removal.
Even though it does work around and with medico-administrative institutions,
QS still reconfigures biopower in important ways. QSers use technologies that allow
tracking to be significantly compressed. Because the technologies are smaller, more
affordable, and able to track passively, individuals are able to collect types of data
previously only available in large-scale population based studies. The n=1 basis for
QS projects allows the data of a single individual to serve as the basis for any
conclusions about health or normative ways of organizing life. A normate subject still
exists, but it is a single individual throughout time that interacts with a particular
environment, not an abstract concept of the normate human created from the average
of large populations to be applied to single individuals. Being "human" in a
Quantified Self sense means adjusting self-care techniques according to a data-driven
picture of oneself throughout time, rather than comparing oneself to an ideal, abstract
human in general. Instances such as when Smarr or Ming* brought their doctors large
amounts of data bring out the changing biopower landscape that QS is a part of.
These three individuals all had data that would allow them to be considered experts
and successfully identified the manifestation of certain diseases, but the medical
industry
*
See previous chapter for Ming’s story.

146
was not set up to incorporate this type of expertise into treatment. Doctors were
unable to understand the data and had difficultly understanding it for the purposes of
treatment and diagnosis. This resulted in Smarr’s condition only being officially
recognized after it had manifested itself and begun to exhibit typical symptoms and
Ming going outside of the medical recommendations to create her own insulin
administration plan for her child.
McCurdy represents a move toward a new treatment protocol that is more
indicative of the changes that QS can potentially implement within the current
structure of biopower. She is able to work with her doctor for more targeted
treatments, but provides much of the data herself and plays a large part in what factors
are examined. Here, she still engages within a system of biopower, but the institution
changes its assessment of McCurdy’s situation largely based on data she collects. The
top-down model of biopower whereby an institution forms knowledge, makes
recommendations based on a norm, and coerces individuals to conform to those norms
with threats of exclusion do not make a strong appearance here. Instead, knowledge
and recommendations form from analysis of the individual and are then integrated into
institutional recommendations for self-care.
Instances such as Daugherty’s project of working on her mood through
mindfulness and attention to smiling demonstrate how this aspect of QS projects can
move beyond the actual site of the clinic to everyday life while still engaging with the
individual. Daugherty collects her own data and directs her experiment, but with the
institutionally-sanctioned idea that being happier more often is beneficial for health.

147
However, unlike McCurdy and others, she does not visit a clinic but rather comes to
this conclusion through a common-sense approach that is influenced by medical
knowledge. Her project represents the potential of QS projects to work within medico-
administrative knowledge, yet outside the physical space of the clinic in a way that
privileges individual data over population-based data.
These projects all represent how biopower can become reconfigured on the
individual level. They also illustrate the changing relationship between patient, data,
and medico-administrative knowledge. But they only take us so far in understanding
how the structure of the institution and the policies that they follow are changed with
the rise in self-tracking and self-care through individual datasets. As the next chapter
will demonstrate, equating the individual with a dataset has larger implications when
medical and governmental institutions also begin to see the individual in this manner.
By quantifying parts of the individual and attempting to improve certain aspects
according to metrics of health closely resembles what Wendy Brown has identified as
a sort of neoliberal logic at work. This logic attempts to integrate market principles
into everyday life and governance techniques. The next chapter will examine what
happens to the relationship between individual and institution when the individual
becomes capital in the form of data.
148
1
Bowden, Mark. "The Measured Man." The Atlantic. Web.
<http://www.theatlantic.com/magazine/archive/2012/07/the-measured-man/309018/>.
2
Larry Smarr on Chron's Disease and Quantified SelfQuantified Self. quantifiedself.com. Web. 13 Feb.
2013. <http://quantifiedself.com/2013/02/larry_smarr_croneshope_in_data/#more-5853>.
3
Bowden
4
Bowden
5
Se Wolf, Gary. The Data-Driven Life - NYTimes.com. www.nytimes.com. Web. 15 Feb. 2013.
<http://www.nytimes.com/2010/05/02/magazine/02self-measurement-t.html?_r=3&pagewanted=all&>,
The ‘So What’ of the Quantified Self | TechCrunch. techcrunch.com. Web. 5 Feb. 2013.
<http://techcrunch.com/2012/03/31/quantified-self-so-what/>, The Measured Life | MIT Technology
Review. www.technologyreview.com. Web. 5 Feb. 2013.
<http://www.technologyreview.com/featuredstory/424390/the-measured-life/>, The Quantified Self:
Counting Every Moment | the Economist. www.economist.com. Web. 5 Feb. 2013.
<http://www.economist.com/node/21548493>, Quantified Self How-To: Designing Self-Experiments.
hplusmagazine.com. Web. 5 Feb. 2013. <http://hplusmagazine.com/2012/11/14/quantified-self-how-to-
designing-self-experiments/>, Know Thyself: Tracking Every Facet of Life, From Sleep to Mood to
Pain, 24/7/365. www.wired.com. Web. 11 Apr. 2013.
<http://www.wired.com/medtech/health/magazine/17-07/lbnp_knowthyself?currentPage=all>, Wolf,
Gary. Quantified Self | Aether. aether.com. Web. 14 Feb. 2013. <http://aether.com/quantifiedself>, The
Quantified Man: How An Obsolete Tech Guy Rebuilt Himself for the Future | Wired Enterprise |
Wired.com. www.wired.com. Web. 11 Apr. 2013.
<http://www.wired.com/wiredenterprise/2013/02/quantified-work/all/>, Living the Quantified-Self
Way: Like a Weirder, Hive-Mindier Weight Watchers | Vanity Fair. www.vanityfair.com. Web. 11 Apr.
2013. <http://www.vanityfair.com/culture/2013/02/quantified-self-hive-mind-weight-watchers>, and
Wolf, Gary. "Our Three Prime Questions." Quantified Self. Web.
<http://quantifiedself.com/2011/09/our-three-prime-questions/>. The largest of these evangelists to
appear is Gary Wolf, co-founder of QS. Though he writes many of the articles that appear in print, the
articles still demonstrate a widespread interest in the movement because of the large readership of the
periodicals and the frequency that Wolf’s articles appear in so many different places.
6
Barooah, Robin. The False God of Coffee | Quantified SelfQuantified Self. quantifiedself.com. Web.
14 Feb. 2013. <http://quantifiedself.com/2009/10/the-false-god-of-coffee/>.
7
Sky Christopherson - Self Quantification and Performance on Vimeo. vimeo.com. Web. 13 Feb. 2013.
<http://vimeo.com/40265860>. Christopherson also used many QS techniques to help the women’s
Olympic track team pursuit team win a silver medal in the London Olympic games. His movie Personal
Gold documents this process.
8
Wolf Quantified Self
9
Welcome to Zeo Sleep Manager | Zeo Sleep Manager. www.myzeo.com. Web. 16 Apr. 2013.
<http://www.myzeo.com/sleep/>.
10
Wolf Quantified Self
11
Wolf Quantified Self
12
Foucault, Michel. The Birth of the Clinic; An Archaeology of Medical Perception. N.p.: New York,
Pantheon Books, 1973. Print. 34
13
Foucault, Michel. The History of Sexuality. N.p.: New York, Pantheon Books, 1978. 138.
14
Rose, Nikolas. The Politics of Life Itself: Biomedicine, Power, and Subjectivity in the Twenty-first
Century. N.p.: Princeton University Press, 2007. 6.
15
Rabinow, Paul, and Nikolas Rose. "Biopower Today." BioSocieties 1 (2006): 197.
16
Wolf "Our Three Prime Questions."
17
"Gordon Bell: Every Beat of My Heart." Quantified Self. Web.
<http://quantifiedself.com/2015/03/gordon-bell-every-beat-heart/.>.
18
"David Joerg: Building My Personal Operating System." Quantified Self. Web.
<http://quantifiedself.com/2014/12/david-joerg-building-personal-operating-system/>.
149
19
"Ben Finn: Improving My Sleep." Quantified Self. Web. <http://quantifiedself.com/2014/11/ben-finn-
improving-sleep/>.,
"How to Track Your Sleep: Learn From Daniel Gartenberg at QS15." Web.
<http://quantifiedself.com/2014/11/qs15-conference-preview-daniel-gartenberg-tracking-sleep/>.,
Christopherson,
Loree, Jewel. "Self-Quantifiers Meetup at Tableau." Quantified Self. Web.
<http://www.tableau.com/public/blog/2014/05/self-quantifiers-meetup-tableau-2478>.,
"Christel De Maeyer: My Journey with Sleep Monitoring." Quantified Self. Web.
<http://quantifiedself.com/2014/09/christel-de-maeyer-journey-sleep-monitoring/>.,
"Kouris Kalligas: Analyzing My Weight and Sleep." Quantified Self. Web. <
http://quantifiedself.com/2014/09/kouris-kalligas-analyzing-weight-sleep/>.
20
"Topic Archives: Videos." Quantified Self. Web. <http://quantifiedself.com/topics/videos/>.
21
Finn
22
"Sleep Cycle." Web. <Sleepcycle.com>.
23
"Sleepio." Web. <Sleepio.com>.
24
Rose and Rabinow 197
25
Foucault, History of Sexuality Vol 1 139
26 "QS Access App." Quantified Self. Web. <http://quantifiedself.com/access-app/app>.
27
"QS Access App."
HealthKit works by consolidating data from a number of different apps and the hardware of the iPhone
itself. However, this data is generally locked into HealthKit and the uses are limited. The QS app
exports this data for people to use. Much like Finn’s project above, the creation of a tool to export this
health data serves to make the individual the expert in their own data.
28
Fox, Susannah. "Visualize This: An E-Patient’s Medical Life History." E-patients.net. Web. <http://e-
patients.net/archives/2012/03/visualize-this-an-e-patients-medical-life-history.html>.
29
Ramirez, Ernesto. "Talking Data with Your Doc : The Patient." Quantified Self. Web.
<http://quantifiedself.com/2012/03/talking-data-with-your-doc/>.
30
McCurdy, Kathryn. "How Visualizing Health Problems Could Help Solve Medical Mysteries."
[sensical]. Web. <https://sensical.wordpress.com/2011/11/16/how-visualizing-health-problems-could-
help-solve-medical-mysteries/>.
31
McCurdy
32
Rose and Rabinow 197
33
Rose and Rabinow 197
34
Ramirez, Ernesto. QS and Mindfulness Quantified Self. quantifiedself.com. Web. 28 Feb. 2013.
<http://quantifiedself.com/2013/02/qs-and-mindfulness/>.
35
Ramirez QS and Mindfulness
36
Rose, “The Politics of Life Itself” 5
37
Stephen Wolfram Blog
38
Stephen Wolfram Blog

CHAPTER 4
Genetic Capital
Quantified Self practices demonstrate how techniques of biopower normally
applied to populations can be utilized on an individual level to produce knowledge
and, in turn, unique subjects. However, these subjects do not entirely escape
involvement with larger institutional structures such as medicine and the government.
As demonstrated in chapters two and three, subjects engaged with the changing
practices of self care still rely on medical knowledge to understand their health and
how their bodies operate with social and environmental contexts over time, even if
they adapt that medical knowledge to their own purposes. In response to the demand
for individual access to medical data, companies like 23andme have emerged to
provide data previously guarded by the medical community. 23andme is the most
popular DNA analysis service, giving users access to a range of variations among
their genes that indicate ancestry and mark certain physical and health-related traits.
On the very basic level, users take the results from a 23andme test and learn about
their susceptibility to a host of diseases and conditions, including gout, alcoholism,
and breast cancer. On a more complex level, users upload their data to services like
OpenSNP where the data becomes publicly available for experiments and testing.1
While 23andme is pitched as a product for individuals to use and learn more
about their genetic makeup, the actual business plan involves more than just selling
kits and providing information to consumers. The results of those tests become an
important revenue stream for 23andme as the company sells access to its large
150

151
database of genetic information. 23andme not only sells access to the database to
outside institutions, it uses the database for their own research studies and, recently,
began laying the groundwork for developing pharmaceutical drugs.2
As 23andme develops the uncharted territory of personal genome testing, it
also has come under fire by the FDA for providing potentially dangerous information.
If a person has access to their predisposition to certain diseases or conditions, there is
the assumption that they will take action to prevent unhealthy conditions from
manifesting themselves, even if the person does not know the medically appropriate
actions to take. This concern about taking uninformed action led the FDA to send a
warning letter to 23andme in November of 2013, requiring them to cease operations
until proper oversight could be established.3
The tension here between individuals wanting information, a company selling
a product, and a governmental agency attempting to establish regulations highlights a
development in contemporary medical technologies where humans no longer become
local instances of diseases (as in Foucault’s history of medicine discussed earlier), but
become reconfigured as capital through the storage, use, and re-selling of their genetic
data. This aligns with Wendy Brown’s warning that market rationality currently
permeates social, governmental, and institutional systems, reconfiguring individuals
as capital and making the maximization of various forms of monetary and non-
monetary capital the primary goal of different spheres of life.4 In terms of 23andme,
this means gathering genetic data about a person to be used in studies to profit the
company later as well as creating users that are concerned with investing in a future,
healthy self.

152
Brown claims that life ordered around market rationality carries with it the removal of
the promise of equality, justice, and freedom that has come to be associated with
democracy. She says that “the cultivation and expression of distinctly human
capacities for ethical and political freedom, creativity, unbounded reflection, or
invention” get pushed aside as life becomes an issue of winners and losers within
deregulated marketplaces each trying to enhance their position at the cost of others.5
The logic surrounding 23andme becomes significant because it provides an instance
thoroughly organized by market rationality and advances the idea of investing in
oneself to make a “better” person, but at the same time it actively encourages the types
of activities that Brown worries about losing in an economically-organized society,
namely the disappearance of a platform of critique that allows instances of inequality
and injustice to emerge.6 Yet, the service does not point to an emergence of a utopian
rule by popular sovereignty or a return to homo politicus, where individuals are
political beings. Instead, individuals utilize information about their genetic makeup to
increase their own health-related capital while simultaneously publishing this
information online for others to use, putting themselves at risk for potential mis-use of
their data for the benefit of other individuals and the general population.
The process of configuring the individual as capital, but in a manner that does
not necessarily circumvent the promise of liberal democracy happens in several ways.
First, 23andme’s model revolves around providing information and guidance to the
user about how to engage with their data, but there is no clear, universal metric for
how the user can increase their capital in a way that can create a common marketplace

153
where capital can be exchanged. Finding out about particular genetic qualities allows a
person to understand more about how their bodies work and engage in practices of
self-care, but these findings are not always accurate or applicable outside personal
development. The second way is through the governmental response to regulate the
service on the side of the consumer. Brown brings up a number of examples where
neoliberal and market logic dictates that governmental decisions play out in favor of
corporations’ rights based on principles of free speech. However, in the FDA’s case
against 23andme, the service was actually paused in order to put in proper regulations
to protect the consumer. The third way is an extension of this obligation to protect the
individual. Some users of 23andme have taken their data and published it online for
anyone to use for research or individual experimentation, putting themselves at great
risk for future misuse of data in exchange for the possibility of helping others. Here,
individuals do not become isolated sites of capital accumulation at the expense of
others, but rather act in shared self-interest and capital accumulation. This chapter
argues that 23andme may create users, corporations, and governments that operate
within a market rationality, but the relation between these entities actually creates a
subject that opens up the possibility for a renewed interest in the “ethical and political
freedom, creativity, unbounded reflection [and] invention” that Brown sees as lacking
within a neoliberal society.
23andme may currently dominate the discourse around personal genomic
testing, but it was not the first company to provide the service. DeCODEme, based in

154
Iceland, was allegedly the first company to offer personal genome testing.*
DeCODEme started in 1996 as an off-shoot of its parent company, deCODE Genetics.
Like 23andme, the price point for deCODEme was initially set at around $1000.
Unlike 23andme, deCODEme leveraged the scientific legitimacy of its parent
company, deCODE Genetics, to appear more reputable while still marketing the
results of the test as interesting or entertaining rather than for diagnostic purposes.7 In
2012, deCODEme was shut down when deCODE went bankrupt and was sold to
Amgen.8
Alongside 23andme and deCODEme, Navigenics was yet another major
personal genome services. This company presented itself as a “sober, responsible
reflection on the information present in its customers’ genomes.”9 The reports
generated by Navigenics provided more detail and more context for users than
23andme while also initially focusing more on the medical side of genome analysis.
Like deCODEme, Navigenics folded around 2012, and was sold to Life
Technologies.10 Of the “Big Three” personal genome testing services, only 23andme
remains, though there are smaller companies that exist. These testing services are
generally relegated to more boutique companies like Knome, which offers full
genome sequencing for around $100,000.11
23andMe works by collecting a vial of spit from each user. The vial is then
sent back to 23andMe, which outsources the actual analysis of the DNA to another
* The first goal of deCODE Genetics was to create a national database of Icelandic genetic data in order
to find genetic factors for common human diseases, based on the presumption that Icelandic people

155
company, Illumina. The data that Illumina sends back to 23andMe contains
information on the mutations within the base pairs of DNA. These mutations are
called single nucleotide polymorphisms, or SNPs, and are responsible for the different
genetic code between people.12 23andme then compares the results with scientific
studies and creates a profile for the user. The profile contains raw information about
the SNPs that have been tested, a note about how reliable the tests are, an analysis of
how likely the user is to have a trait or condition, and some rough suggestions on how
to prevent the condition if it is a debilitating medical issue.
One of the more obvious uses of 23andme’s health-related data is to anticipate
the emergence of future health conditions that range from various forms of cancer to
schizophrenia to gout to sickle cell anemia to Tourette’s syndrome.13 Providing this
type of information lends itself to users taking precautionary measures to ensure a
healthy future, as evidenced by the a section labeled “What You Can Do” in the
results section of the user’s account that provides a rough guide for actions a person
can take to avoid or minimize the onset of some conditions. This usage seems to
reflect Brown’s main claim that individuals are increasingly concerned with
improving themselves in the present as an investment in a better future self. In
everyday life, individuals become what Brown calls homo oeconomicus, a person
concerned with maximizing different forms of capital through their activities, whether
it is “education, health, fitness, family life, or neighborhood.”14 Institutions reflect this
change as well. Online dating sites, schools, gyms, and other businesses claim “the
were fairly genetically homogenous. The project was bound up with a host of ethical, political, and

156
importance of maximizing return on investment of affect” while governmental entities
like the Supreme Court characterizes “free speech as the right to advance or advertise
one’s worth without this worth being monetized.”15 For Brown, the dominant logic in
contemporary, neoliberal Western society comes in the form of the marketization of
all activities – including those informed by genetic predispositions.
She outlines three main characteristics of homo oeconomicus.16 The first is that
homo oeconomicus is always and everywhere homo oeconomicus. Subjects are always
configured in economic terms and never as alternative types of subjects, such as
political subjects. The second characteristic is that the homo oeconomicus subject
becomes human capital looking to increase its value and competitive position, rather
than engage in exchange or interest. By this she means that individuals have begun to
find ways to improve themselves for the future. By way of example, she foregrounds
a number of cases that include “investing” in a liberal arts education (rather than
learning for its own sake) in order to enhance one’s future marketability or investing
in one’s appearance in order to attract a partner. The third characteristic is that
financial or investment capital becomes the primary model for homo oeconomicus, in
place of productive or entrepreneurial capital.17 Subjects are less concerned with
creating actual products or engaging in exchange to increase forms of capital. In place
of this productive and entrepreneurial model, subjects perform actions that seek to
increase the future value of the self. For Brown, examples of these actions include
gaining social media followers and likes, gaining a ranking for all different types of
social criticisms.

157
activities, and education or certification for certain skills. Importantly, the logic of
investment causes decisions about “education, training, leisure, reproduction, [and]
consumption” to be judged solely in terms of how well they can increase the value of
a future self.18
The pervasive logic of homo oeconomicus has not only set the stage for
products like 23andme that allow individuals to find areas of themselves to work on
with the hope of increased health metrics. That logic is perpetuated through the service
itself. The test results configure the user as a set of genetic data that could be desirable
because it has a low percentage chance of manifesting a condition or undesirable
because of an increased risk of certain unhealthy conditions. Within the service, users
are reduced to this profile of potential conditions that can be manipulated for a future
healthy self, removing other aspects of the self such as personality, general happiness,
social or cultural connections as indexes of health and happiness.
Beyond the self-creation of the user as homo oeconomicus, Brown claims that
“we are human capital not just for ourselves, but also for the firm, state, or post
national constellation of which we are members.”19 The logic of capital accumulation
moves throughout the individual and any surrounding institution or social structure.
This move appears within the business model of 23andme when the personal data of
users is configured as potential financial capital and sold to other companies. 23andme
may be the main service left within the field and have a large number of users, but it is
not without financial issues. The company is not currently profitable, running off of
over $126 million of investment funding from companies like Google and investors

158
like Russian billionaire Yuri Milner, who has funded Facebook, Twitter, and
AirBnb.20 The personal tests each cost $199, but they are not the main source of
income that 23andMe hopes to cultivate. 23andMe aims to get as large a data pool as
possible in order to license out that information to research universities and other
organizations. Companies like 23andMe have already worked with the Parkinson’s
Institute and Autism Speaks to further genetic research on those respective diseases.21
In a similar manner to the way Google and Facebook collect user data for advertising
purposes, 23andMe hopes to make the genetic data of its users a product for other
companies. Immediate results of this business model have culminated in a number of
published papers by 23andMe researchers. These include informational facts like
identifying the SNPs related to a person who identified a soapy taste in cilantro or
genetic variants that lead to linked eyebrows (commonly called a “unibrow”).22 Other,
more medically oriented studies have included identifying personality and health traits
that appear alongside Parkinson’s disease and linking certain ancestries with
Parkinson’s and skin cancer.23
As Lenzer and Brownlee point out, “in a clever reversal, companies are getting
research subjects to pay—rather than be paid—to become research subjects.”24 Not
only are the users of 23andme potentially engaging in self-creation along the lines of
investing in a healthy, future self, they are becoming human capital for researchers and
experimenters investing in the future of medical knowledge. Though increasing future
health may seem like a worthwhile goal, Brown raises the concern that if humans
become capital for institutions concerned with their own survival, the subjects are not

159
guaranteed any form of security or protection. Many analysts have voiced similar
concerns with the data collected by 23andme. Individual data may be lumped with
genetic information from other people and anonymized, but that data can still be used
by a variety of researchers without approval from the individual. Once the customer
submits their spit for analysis, they essentially write off their ability to control what
happens to that data their spit generates. An even larger concern is the unpredictability
of future genetic research. Current 23andme users also waive their rights for their data
to be excluded from future research: they waive their rights to inclusion in research
that does not yet exist but could involve any number of ethical, profitable, or
personally questionable areas.
For Brown, market rationality may underlie the structure of 23andme and its
potential uses, but her worries about the larger effects of that rationality do not
necessarily follow. She brings up the concern that “all market actors are rendered as
little capitals (rather than as owners, workers, and consumers) competing with, rather
than exchange with each other,” a situation where the individual becomes not just
isolated, but acts in a way that opposes any sort of collective action.25 While the user
of 23andme does become a “little capital” through a unique genetic profile and
various design choices within the 23andme interface, the scope of 23andme’s
suggestions and the limitations of data application fail to create a larger marketplace
acting as a zero sum game and Brown’s concern of homo oeconomicus as inherently
competitive does not necessarily emerge.
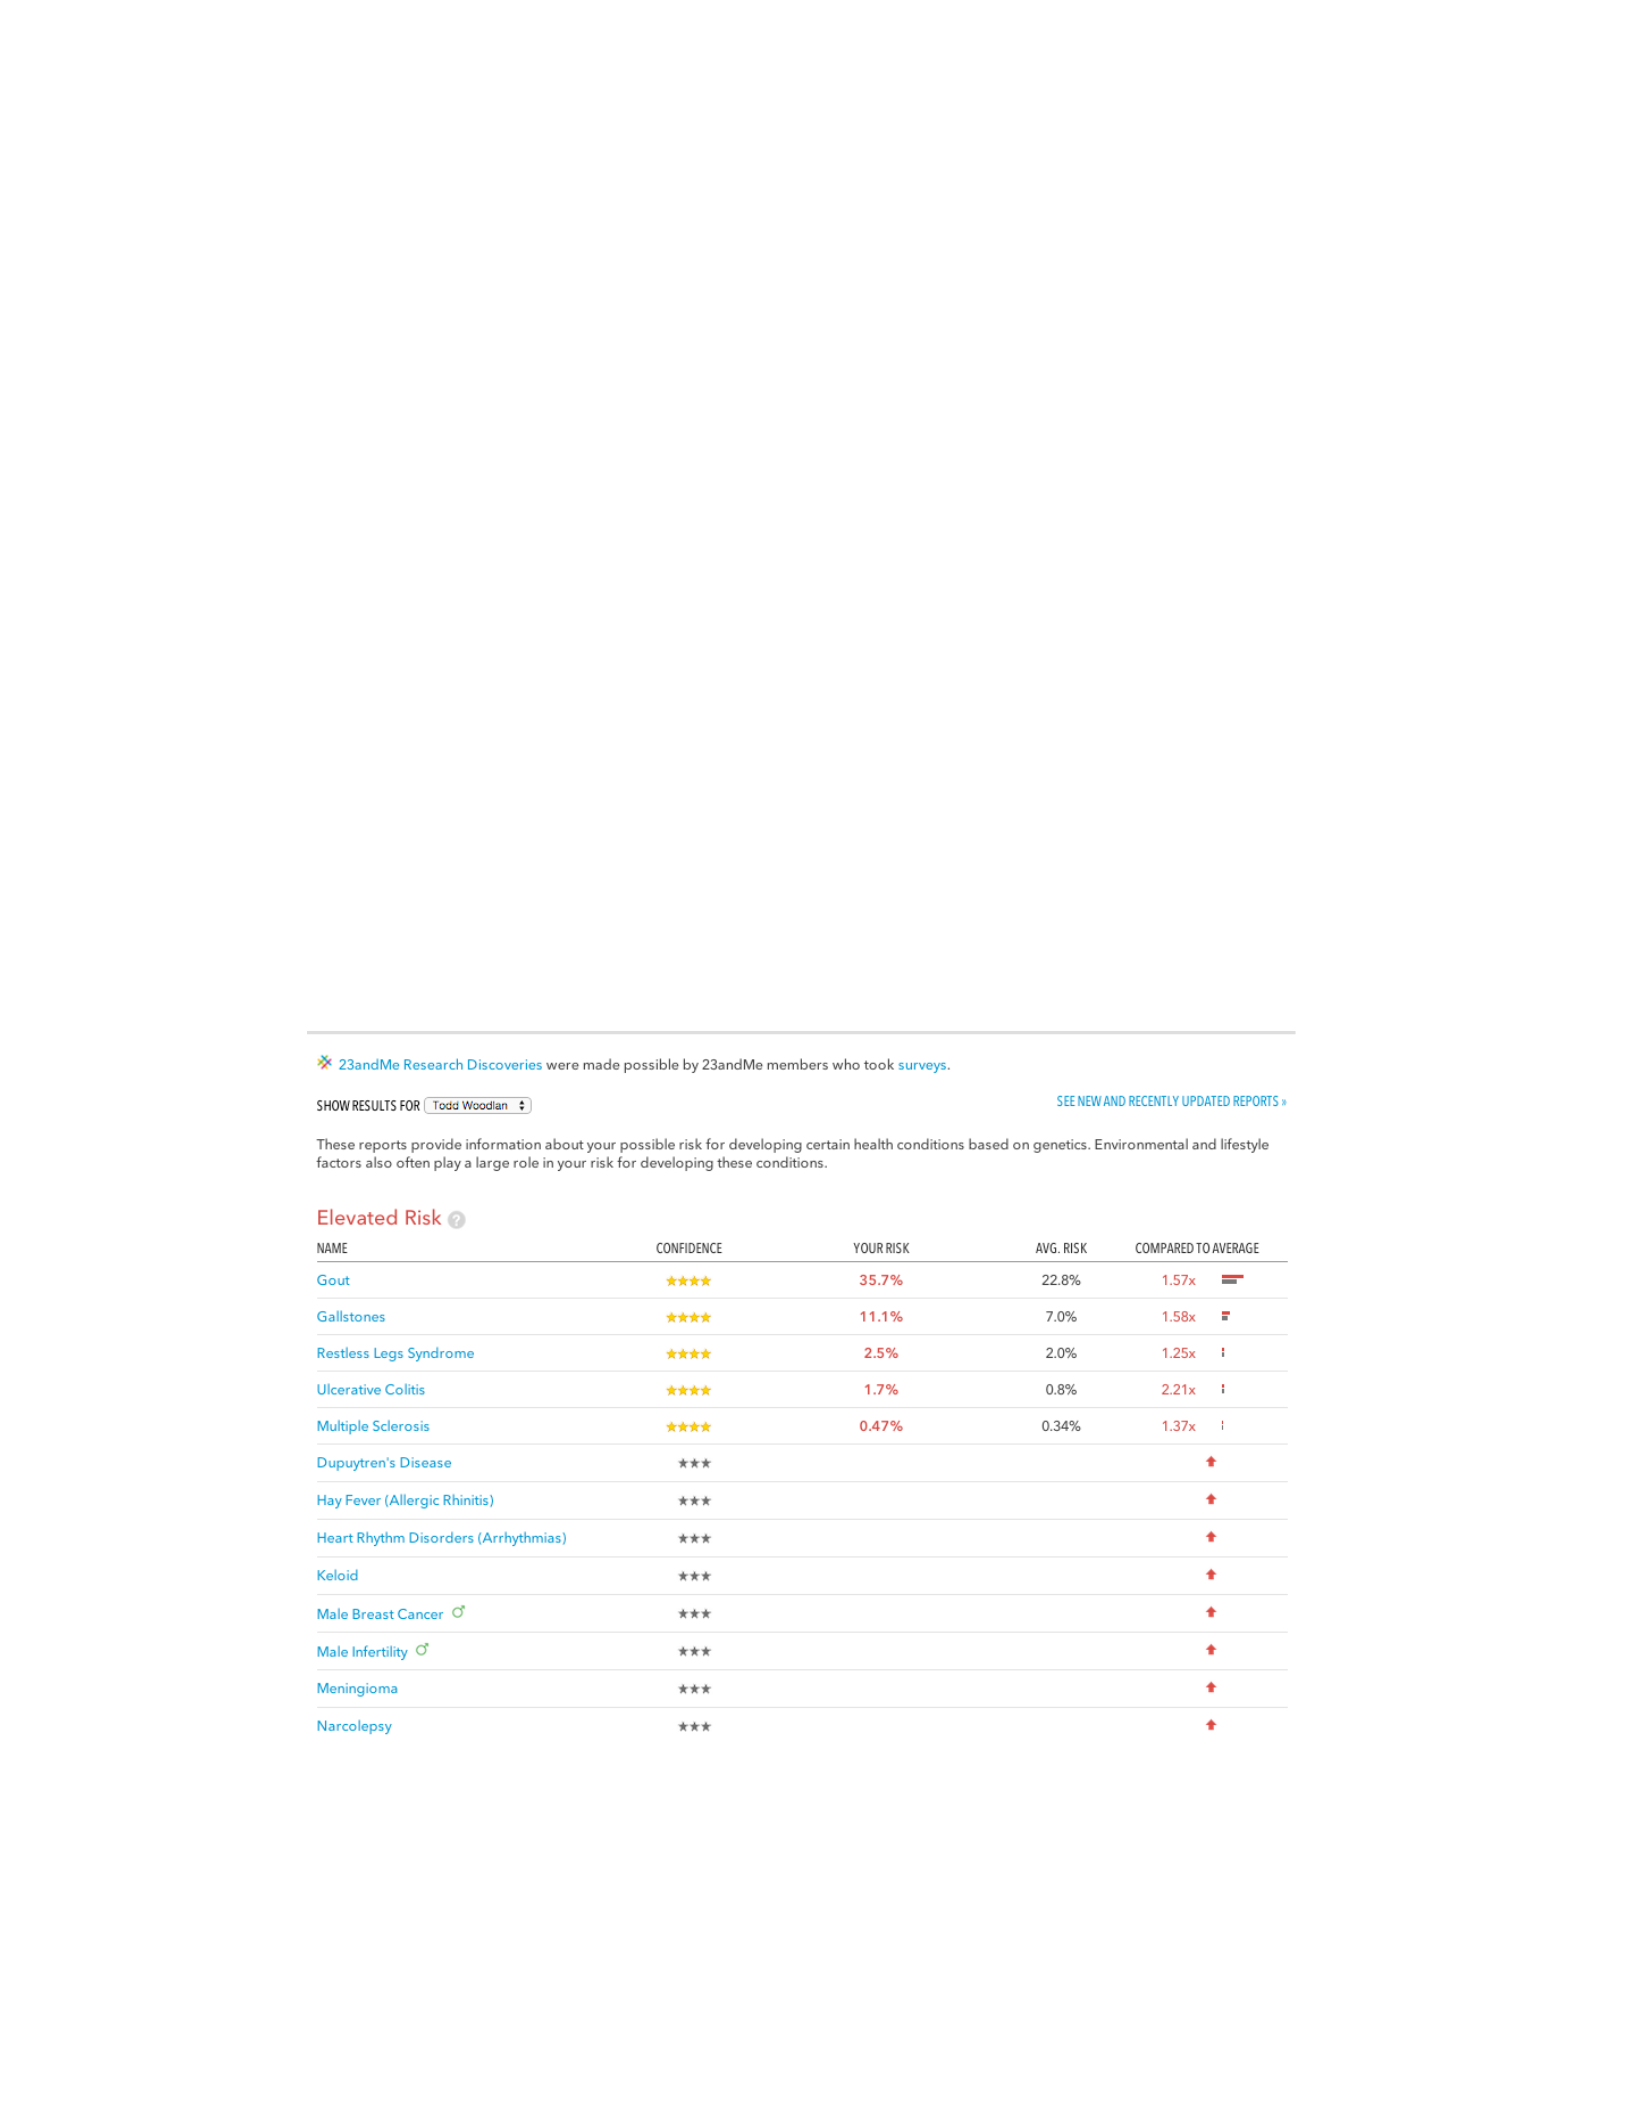
160
23andme’s organization encourages users to pick their own method of
incorporating the data into their daily practices. Each page shows results of the rest in
a way that provides the raw information about genomes that affect certain physical
characteristics, drug responses, inherited conditions, and health risks and very little
guidance as to how to use the information. On the pages for each individual genetic
trait, 23andme shows relevant studies, a brief assessment of the data, an explanation
of the condition, and a rating designating how solid the findings appear to be. In the
case of potential health risks, a short list of things the person can do to prevent the
condition is presented alongside the other information. Each condition is tied with
columns that show how reliable the related studies are, the user’s risk, the average
risk, and a comparison with the average risk:
Figure 13: 23andme heightened risks
https://www.23andme.com/you/health/risk/

161
Clicking on a condition gives an overview of the condition followed by the user’s
results as a percentage chance of getting the condition, an explanation of the results,
and suggestions for how to decrease the risk of developing the condition. The
presence of an “average risk” contextualizes the data within a larger population, but
does not position the members of that population as potential competitors. If an
individual’s risk is small or decreases through some action on their part, the overall
average risk of the population remains functionally unchanged. Likewise, if the
average risk of the population decreases, it does not come at the cost of the individual.
Information about the larger population does not become an analysis of competitors,
but a way to situate one’s own susceptibility to a condition.
A tab at the top also allows direct access to the actual markers that appear in
the user’s genome as well as a brief summary of what those markers mean. In the
23andMe interface, the user can see the relevant data, but only has a brief
interpretation and no clear guide for how to use that information within a set of
practices. The service may be a “medical device” in terms of engaging with medical
knowledge, but it still remains an “information product” in the sense that it does not
show a set of best practices or regime of self-care, leaving that decision up to the
user. The service leaves much of the techniques of self-care open for interpretation by
the individual. For example, the suggestions for avoiding gallstones appears as:
162
Figure 14: 23andme recommendations
https://www.23andme.com/you/health/risk/
The first suggestion, maintaining a healthy weight, does not outline specific
parameters for what a “healthy weight” means or how much physical activity the user
should engage in. Rather, it serves as a starting point for the user to research more and
act on their own. Though this information is an interpretation of the data and a
parameter in which self-care can be enacted, it is also partial. The user cannot act on
this information alone, but must actively search for more specific guidelines on how to
avoid gallstones. The last three points – learning family history, connecting with
relevant groups, and talking with a genetic counselor – also providing starting points
for action and not specific guidelines in and of themselves.
On the one hand, these suggestions seem very much to fit into Brown’s claim
that market rationality substitutes top-down commands and orders with “best
practices”. The term “best practices” refers to “organically gestated procedures
validated by experience and success,” or a flexible trial-and-error procedure that gets
developed over time.26 Instead of a strict set of rules or steps that an individual must

163
take to perform a task, best practices are a constantly updating collection of
recommendations on how to engage in a task. These recommendations change as they
are tested and new methods are discovered, but they are always evaluated according to
how well they increase capital for the future. Best practices are an issue for Brown
because they are not industry-specific and can move fluidly between different spheres,
potentially infiltrating political life and causing it to operate among market principles,
assessing politics according to how well it creates value for the future and maximizes
competitive advantage.27 Positioning decisions in this way de-politicizes decisions by
appearing objective, even though there are assumptions made about what is “best” that
can potentially alienate groups of people. Best practices can be overturned by better
practices, but the end goal or underlying logic cannot be questioned because the
practice itself is value-neutral and justified through experience.28 Additionally, not
only does politics become organized according to market principles, it actual
dissipates into the market itself, removing “the need for legal, political, or ethical
interference from the state or any other source.”29 When overall return on investment
becomes the primary concern, politics does not become concerned with the well being
of its subjects in terms of justice or equality.
Again, 23andme would appear to fall in line with Brown’s assessment. The
data presented through the service does not create a solid set of rules or regulations.
The user only sees their chances of getting a disease and a rough guide as to how they
should proceed. The user has to formulate their own protocol for becoming healthier
through the revelations in the data, test it on their own, and modify it according to

164
their findings as they would when formulating best practices. Though 23andme may
encourage a critique and revision process with regard to practices, the scope of the
resulting practices becomes limited to only the individual, an important point that
would make a large-scale application of any set of best practices developed through
23andme data difficult.
Best practices assume the flattening of “government, business, and knowledge
endeavors” into a single, market-driven episteme that provides recommendations for
individuals to follow.30 23andme not only configures the interface so that the
individual must engage in the process of collecting and assessing information on their
own, it also actively fragments different forms of knowledge, rather than attempting to
condense these forms into an organic whole. 23andme performs this dispersal of
information because of the shaky, contextual, and inconclusive nature of the test
results that has caused them to push the user toward other sources of information to be
able to make sense of the data. Though the genetic map of a person can be read
through 23andMe’s DNA sequencing, creating the entire map is very expensive and
understanding what that map means proves very difficult. There are millions of SNPs
and research is still underway to determine the connection between particular SNPs
and the expression of certain traits or the manifestation of diseases.31 Schwartz points
out that genetic tests like 23andme do not provide conclusive evidence of diseases or
traits belonging to a person:
The information provided by such companies is based on studies—of
more or less validity and reliability—of associations between specific
single-nucleotide polymorphisms and individuals’ risks and
characteristics (Fox 2008). Such genetic information is necessarily

165
partial even if it is valid: a patient with below-average genetic risk of
lung cancer may well have higher-than-average overall risk, due to a
heavy smoking history. There is basically no evidence at present that
these sort of genetic tests contribute to health or improve healthcare.32
This observation by Schwartz brings to light the inconclusiveness of the tests. Though
the tests do reference some scientific studies and illuminate some interesting
information about a person’s genomic profile, there are many more factors that
contribute to the expression of traits found within gene variations. The process
becomes even more complex when multiple SNPs are connected to a trait, often with
differing effects on the expression of that trait. For example, one SNP connected to
Type 2 diabetes has been shown to increase the risk of diabetes by 17 percent.
Another SNP decreases the risk by 15 percent.33 Figuring out how to average these
risk percentages out to a number that the consumer can easily understand is one of the
difficulties for 23andMe. An early interview by Wired magazine quotes the 23andMe
founder as stating that, “A lot of this is unknown. It's totally experimental. …No one
has looked at all eight diabetes markers together. They've all been identified
individually, but they don't know exactly how they work together."34 In the case of
the diabetes-related SNPs, 23andMe decided to multiply the risks together, though
other methods advocate adding the two risks together.35 Because of the large number
of factors that go into identifying a correlation between SNPs and traits, 23andMe has
to choose which SNPs to test, providing results to the consumer that require the
consumer to assess the legitimacy of the results on their own and figure out how the
data can best be used.

166
Even with the varying reliability of different markers, 23andMe chooses to
give the user as much information about their genome as possible, a process that
competing companies have called into question. Parthasarathy points out that
23andMe tests for a particular SNP as soon as there is research connecting it with a
trait or health condition.36 Other companies, like the now defunct Navigenics, have in-
house scientists do an internal review of the scientific literature before adding a SNP
to their tests to ensure that the studies connecting SNP with a condition are reliable
and consistent.
In addition to the choices made about which SNPs to analyze, genomes
themselves do not completely determine particular characteristics or are not
necessarily a good indication of certain health risks. Ethicist George Annas points out
that family history is often a better way to determine if a person will develop a
particular disease.37 Other researchers have also noted that the interaction between
environmental and genetic factors play a significant role in disease development,
especially for neurodegenerative diseases.38 This points to an odd tendency within the
discourse around personal genomic testing: the medical community upholds the
humanistic clinical and laboratory structure of medicine by claiming the authority of
studies while also presenting a type of subject that cannot be understood by clinical
medicine. If genetic markers had a 1:1 correlation with the expression of traits and
conditions, it would be a straightforward case where clinical medical knowledge
about a user’s genome could be used to determine aesthetic traits like hair and eye
color; informative aspects of the patient like whether they can taste cilantro; and
important

167
health traits like whether or not they will develop breast cancer. Here, these traits and
health conditions would not rely on the individual patient, only the processing of the
necessary information that was extracted from the body of the patient and run against
the findings of particular studies. Yet, the arguments against 23andMe from the
medical community claim that this process isn’t possible with genetic information.
The admission that family history and environmental factors play a large role in
illness requires the inclusion of the individual patient and their surrounding
circumstances in order to properly understand genetic information. The arguments
from the medical community against 23andMe suggest that it is actually impossible to
diagnose or understand genetic information without also understanding the contextual
situation of the patient themselves. As with the shift to posthumanism, there is a shift
from the user that can possess an objective set of “good” characteristics toward a user
that is at the nexus of a number of different environmental, social, and cultural factors
that make it difficult to generalize the worth of an individual according to universal
standards.
The variable reliability of conclusions drawn from the genetic tests and the
relatively lax standards by which 23andMe add SNPs and utilizes contextual
information has implications for the responsibility of the user. The “evidence” links
on the 23andme results point to the US National Library of Medicine, the “My Family
Health Portrait” link goes to the Surgeon General, and the “International Foundation
for Functional Gastrointestinal Disorders” link directs users to a nonprofit
organization that is partially funded by the National Institute of Health. In each case,

168
the user is pointed away from 23andMe toward a medically sanctioned information
source that may or may not agree with the 23andme results, requiring the user to make
their own decisions based on their knowledge of their own situation about what
information is applicable. The test results for each individual position genetic
information not as describing qualities inherent in the patient, but as potential facts
about the individual that may or may not be true and may or may not be applicable to
their life. 23andme encourages the user: (1) to become engaged in learning about
oneself for its own sake and (2) to provide their own set of guidelines on how to
handle their health. The user must create their own regime of self-care by picking and
choosing elements from different areas of knowledge (medico-administrative,
23andme test results, etc.) and evaluating them according to their own unique
circumstance, a process of creating an individual set of best practices for health
management.
In this instance, the company relies on the institutional medical knowledge
and points the user back to the medico-administrative institution for a definitive take
on the information they’re provided while also encouraging the user to create their
own method of interacting with the data. 23andMe pushes the user to work alongside,
but not within, the medical institution and take into account their own unique situation
when deciding how to proceed with their genetic data. Such a user begins to resemble
Kant’s ideal Enlightenment individual discussed in earlier chapters who acts on its
own without the guidance of others, demonstrating the potential manifestation of
Kant’s mature Enlightenment subject within the neoliberal project.39 The user of

169
23andme is encouraged to make their own decisions based on their own research and
not take any data at face value, no matter if it is presented by 23andme, the medical
community, or a support group. However, Brown would point out that the user’s
resulting critical engagement still has the ultimate goal of investing in future health
and attempting to modify the body to become “healthy” according to medico-
administrative standards, even if the specifics of those standards have some
flexibility.
Beyond the 23andme interface itself, the service allows individuals to
download their genetic data. Dozens of other services have been created to provide
alternate ways to analyze the data according to different metrics, newly released
information and studies, specific mutations not found in the 23andme report, and other
areas.40 Because of the ability to process the data in other ways, users are given the
option to investigate and learn about the data more than they would with a restrictive
service that holds all of the data on their servers or, even more extreme, only allows
for a proprietary interpretation of the data to be accessed by the user. As with the
inclusion of outside sources of information and the lack of a specific, 23andme-
sanctioned format for formulating one’s regime of self-care, the ability to download
data point to a move toward giving the user the ability to make their own set of best
practices by engaging with the data.
Pushing the 23andme users to make their own decisions also points to an
underlying logic that the creation of identity through “best practices” does not rely on
a uniform, agreed-upon standard of what is “human.” If users must construct their
own plan for using their genetic information, it means that not only the user’s goals,
but

170
also the manifestation of that user’s ideal identity is highly personalized and situated
among genetic, environmental, and social factors. The quest for what makes up the
human as a universal concept in humanism shifts throughout 23andme and such a
quest is instead replaced by a prompt to create a singular and unique individual with
its own goals and understanding of genetic data, much like the QS projects in chapter
three. The individual, by being reconfigured as capital through a set of best practices
based on genetic data, then becomes a unique entity while still existing under the
umbrella of the human.
23andme’s opening up of data interpretation by providing information rather
than diagnosing illnesses or recommending prevention programs is a purposeful move
that stems from their ongoing issues with the FDA, a legal back-and-forth that appears
to reign in unauthorized interpretation of medical information by users but actually
serves to give a governmental stamp of approval onto the service. On November 22,
2013, the FDA sent a letter to 23andme demanding that it stop selling its genome
sequencing kits without approval. Even though the company had been in business for
several years at that point, in 2013 the company began to increase marketing efforts
pushing the health aspects of the test. For the FDA, this was a very significant shift
that would classify 23andme as a “medical device” rather than an “information
product.” The FDA’s statement claimed that 23andme was “a device…because it is
intended for use in the diagnosis of disease or other conditions or in the cure,
mitigation, treatment, or prevention of disease, or is intended to affect the structure or
function of the body” and required that it go through the same approval process as

171
other medical devices. Ultimately, the FDA approved 23andme to operate as an over-
the-counter device in October of 2015.41 These included carrier status reports on
inherited conditions like Cystic Fibrosis, Sickle Cell Anemia, and Hereditary Hearing
Loss.
Such an intervention on the part of the FDA is significant because it brings to
light the ways that corporate interests end up being supported by governmental
organizations that are supposed to be put in place to protect citizens. By appearing to
engage in the areas of medical diagnosis and disease prevention, 23andme attempted
to speak with the authority otherwise reserved for medical professionals without
actually being a medical entity. It could allegedly identify diseases before they
manifested themselves within individuals and could suggest steps to avoid the disease.
These actions were previously situated squarely within the domain of clinical
medicine, which had a monopoly on the creation and interpretation of knowledge
pertaining to disease. As 23andme attempted to use medical knowledge in a
unsanctioned manner, the already existing medico-administrative institutions – led by
the FDA – demanded that it conform to the structure of that knowledge via oversight
by the medical community and government.
Additionally, the FDA is not a medical institution but a governmental agency
put into place to “[protect] the public health by assuring the safety, efficacy and
security of human and veterinary drugs, biological products, medical devices, our
nation’s food supply, cosmetics, and products that emit radiation.”42 A large part of
this stated purpose is ostensibly to curtail any medical practices that could be harmful

172
to the general population of the US. Nonetheless, the FDA works in tandem with
medical institutions to organize society according to parameters set by the medical
community and, in the case of 23andme, by corporations dealing with medical data.
As evidenced by the note to 23andme, the FDA tries to ensure that any entity
operating with reference to medical knowledge is supervised and does not provide
“dangerous” advice to people.
23andme’s designation as a medical device and the late 2015 approval of
certain tests by the FDA with little changes to the presented data demonstrate the
problematic situation that occurs when individuals and companies outside of the
medical profession create and analyze medical knowledge in non-sanctioned ways.43
Such a shift moves the formation of medical knowledge outside of the bounds of the
clinic, the location that Foucault and others have identified as the source of medical
knowledge from the 18th century onward. In the clinic, disease and other conditions
could be studied without the interference of the “extra ‘noise’” found in the home or
other non-isolated locations.44 The context of everyday life was bracketed within the
clinic, which provided a controlled, sterile environment within which disease would
be examined and understood. Within this context, the patient was not an individual
and unique entity, but rather a location upon which disease manifested itself.45 By
entering the clinic, the patient became primarily an object that could be examined
under the medical gaze to find out information about a disease. Studying the
individual patients did not reveal anything about the person themself, but facts that

173
could be added to a body of knowledge surrounding a particular disease, which in turn
was abstracted from the context of everyday life surrounding it.
With the rise of personal genomics testing, assessment of the patient moves
from the sterile and secluded location of the clinic back to the home and is overseen
not by the medical experts, but by the patients themselves, regulated by governmental
organizations like the FDA. In the case of genetic testing, not only does the test itself
move beyond the clinic walls through commercialization, the information becomes
utilized by institutions and individuals in an economic manner. Bandelt et al point out
that in personal genetic testing, “the commercial utilization of many scientific
advances is unfortunately not only frequently out of step with the cutting edge of the
science itself but also several steps ahead of the governmental and social regulations
that the use of these advances require.”46 In these tests, the consumer not only engages
with genetic information without direct oversight, but also accesses information that
may or may not line up with medically-sanctioned knowledge.
The division between FDA and 23andme illustrates Brown’s claim that in a
market-driven, neoliberal society, knowledge becomes part of a single network of
government and corporations. However, the division complicates her claim that law
becomes subject to business interests rather than protecting citizens and that the main
danger of the homo oeconomicus age comes when concern for public good and
citizenship disappears.47 As market rationality covers over all aspects of life, the
political sphere becomes affected as well. Liberty, equality and freedom are no longer
portrayed in terms of the freedom for self-rule or equality among people. Overlaying

174
market principles onto political discourse changes these to mean a freedom of
economic exchange, liberty to pursue increase in capital, and equality through lack of
regulation. Such a shift causes the governmental and regulatory institutions to no
longer be concerned with protecting the individual but instead focus on corporations,
allowing them to write laws and operate with little oversight and regulation.48
Humanism disappears, replaced by a focus on human capital.49
Brown examines four court cases demonstrating the erosion of popular power:
Citizens United v. Federal Election Commission (resulted in large corporations being
able to finance elections), AT&T Mobility LLC v. Concepcion (decreases the ability of
workers to come together to fight corporate abuses), Wal-Mart Stores, Inc. V. Dukes et
al (restricts private and public sector workers’ ability to cooperate), and Ozanne v.
Fitzgerald (also restricts ability of private and public sector workers to band
together).50 According to Brown, these decisions are an indication that “more than
merely being abandoned, legal supports for popular power are discursively identified
in neoliberal reason as unacceptable blockades in a (mystical) free market.”51 The law
here becomes less concerned with promoting the wellbeing of citizens and more
focused on assuring the ability of the market to function without restriction. The most
egregious instance of this privileging of market forces occurs in Citizens United,
where speech becomes reconfigured as capital, whose flows must be protected even at
the cost of individuals’ free speech. As Brown reads it, the Citizens United decision
equated speech as capital that must be protected by claiming that speech
“proliferate[s] and circulate[s]” in ways that can “be wrongly impeded and

175
encumbered, but never quashed,” that it “is the capital of the political marketplace”
which “circulates freely only when corporations are not restricted in what speech they
may fund,” that speech is “innovative and productive, just as capital is,” and that it
“the power of speech and the power of government [are] in direct and zero-sum-game
opposition to one another.”52 Speech, an important medium for political expression
and engagement for individuals, becomes reconfigured as capital that can be
accumulated by both corporations (as persons) and individuals. Speech also becomes
subject to the same logic of market rationality whereby any form of government
restriction becomes an impediment to the “dynamism, innovativeness, and
generatively of speech.”53 In this way, not only does law become a vehicle to protect
the free market, but, even more concerning for Brown, legal decisions use this logic to
make citizens vulnerable to entities with more money and more influence.
23andme provides an alternative example to Brown’s concern about market
rationality taking over legal decisions because the FDA’s intrusion into the operations
of 23andme purport to limit the speech of 23andme in order to protect citizens. Yet,
the eventual loosening of the restrictions on 23andme that allow them to provide the
data from some tests essentially unchanged fails to really limit 23andme’s speech in
practice. Unlike Brown’s examples, however, the ability of 23andme to offer genetic
information about traits and characteristics (not just ancestry information) also
removes restrictions on information that users can have about their own bodies.
Within this situation, both the company and the user gain a degree of free
speech and unrestricted access to information, but the user takes on a particular risk

176
that the company does not. In addition to the risk of potential future abuse of the
user’s data, the user’s risk that forms the basis for the FDA’s ongoing main concern is
the inability of the consumer to properly assess genetic data without a professional,
causing the potential for extreme or unreasonable action on the part of the consumer as
they take on the ability to interpret medical data. Without proper medical knowledge
or a context to interpret that knowledge, the medical community feared that the
individual would engage in certain risky behaviors or fail to take proper steps to
prevent certain diseases. Examples of this include users that find themselves at low
risk for a condition such a lung cancer continuing to smoke cigarettes or users that find
themselves at high risk for breast cancer having expensive and risky mastectomies.*
The FDA’s letter spoke to this when it claimed that, “serious concerns are raised if test
results are not adequately understood by patients or if incorrect test results are
reported” and elaborated that the patients may attempt to improperly manage a disease
or become noncompliant during treatment because of test results.54 Additionally, when
a user finds out their own genetic data, they also gain some insight into the genetic
data of relatives, some of whom may not wish to know about major conditions like
breast cancer. Professionals in the medical field echo these sentiments, agreeing that
the personal genome tests could have some utility in medicine, but would require
professional oversight by a genetic counselor because of the potential danger they
pose to individuals and their families.55 Positions differ as to whether the individual
* Angelina Jolie is a very high profile case of someone who had a double mastectomy after getting a
genotype that pointed toward a high probability of breast cancer.

177
should have direct access to the results coupled with counseling or if the individual
should only be allowed to receive the counselor’s analysis of the results.
Here, the issue of who is free to interpret the data is present, but another issue
arises: that of the user’s reaction to the data. The major fear is that improperly
interpreted knowledge will make its way to the individual and cause them to react in a
way that is either unnecessary or harmful to themselves. On the institutional side, and
often in tension with arguments advocating restricted use of genetic tests, the FDA
and medical communities appeal to the obligation of doctors and government to help
patients. The tests do provide more information about the patient and bring up ethical
issues within medicine about the requirement of the doctor to inform the patient about
potentially harmful conditions, even when the reliability of the personal genome tests
are sometimes shaky. Analysis within medical institutions in response to the FDA’s
warning and rise of personal genome testing rarely calls for an all-out ban on the tests,
but rather a re-working of both how the data is presented to the patient from the
company providing the test and how the medical institution is set up to handle the
data. Patients with access to data can provide more information to doctors, but at the
same time the doctors must be trained to be able to walk through the data with the
patients. At the moment, interpretation of genetic data is not a highly developed skill
in many medical professionals, though many medical scholars have called for this
type of knowledge to be required learning for new doctors
The reorganization of access to and distribution of information in personal
genomics testing points to a move whereby legal, medical, and individual entities may

178
act in a decidedly neoliberal manner that protects the open market, but in a way where
corporate and individual interests are not necessarily directly opposed. When patients
can look at their own SNPs and evaluate the validity of studies on their own to create
individualized treatment plans, they take on a risk of misusing that data, but they also
have the possibility of identifying diseases or conditions before they become an issue.
As the 23andme customer becomes the main assembler of their own risky self-
care practices, user groups have emerged that act in direct opposition to Brown’s
warning that Enlightenment principles of justice, ethics, and critical inquiry disappear
as homo oeconomicus becomes concerned only with its competitive position within a
zero sum marketplace. Many 23andme users voluntarily share their genetic data,
consciously taking on additional risk to themselves with the hope of helping others
understand their genetic data, becoming part of a larger research project, or possibly
gaining more insight into their own genetic makeup through engagement with others.
Websites like OpenSNP, Harvard’s Personal Genome Project, DIYGenomics, and
SNPedia promote their service by stating that users can contribute their genome to, as
in OpenSNP’s tagline, “learn more about their results, get the latest primary literature
on their variations and help scientists find new associations.”56 Superusers armed with
their genetic data upload their data to servers where it is combined with the data of
other people and made available to anyone that wants to access it. These can include
institutional researchers as well as hobbyists who have no professional training.
Participating in these genetic social networks may increase one’s own capital
through the promise of beneficial genetic discoveries or social position within a

179
community of other uploaders, but it does so only obliquely. Though they are
potentially participating in wide-scale research projects that could result in discovering
the root cause of diseases or increasing the health of the population, there is little
immediate benefit for an individual user. In many services, the data could be
downloaded by someone without participating and there is no monetary compensation
for uploading data. The data is not explicitly tied with a real-world identity, so there is
no individual recognition of participation. Stephen Friend, the director of the open
science-supporting non-profit Sage Bionetworks, says that genome sharing systems
“imagine a system where the patient says, ‘I want my data. I want it open. I want
researchers to work on it. I want them to share it.’” The vision here is a network where
individuals donate their genetic information as an obligation to help researchers and
other individuals looking to learn from their genetic information. Contributors share
their genetic data in order to aid in the potential creation of new discoveries or cures
that would benefit the population at large, a move that shows an obligation to care for
one’s neighbor rather than to engage in cut-throat competition with them.
This sense of obligation comes at a cost to the user, however. OpenSNP, for
example, provides a bullet point list of potential complications that could arise from
sharing genetic data through their service:
• Data uploaded to the internet can not be fully deleted, there may
always be a backup somewhere
• By publishing data you expose information about you and your next
of kin worldwide
• Genetic and medical information can be used by employers, insurance
companies and the government to know more about you than you
would like

180
• New findings about your genotypes can be negative57
As with many of the privacy issues mentioned above, OpenSNP warns of exposing
information about oneself and one’s family, workplace and insurance-based
discrimination based on the data, distressing information about oneself, and unknown
future consequences. Yet, even with these warnings, OpenSNP has over 4,000
registered users and 2,400 users with uploaded data.*
The formulation of the risks of uploading genetic data versus the benefits
demonstrates a shift in what can be considered threatening to an individual. The
potential risks listed by OpenSNP and other commentators on privacy are not harmful
in and of themselves. A digital backup of genetic information or even a fully-
accessible public record of someone’s genetic makeup does not immediately cause
harm to an individual, even though those are the types of concerns that are explicitly
brought up. Instead, the use of that information has the potential to create the most
harm. Employers and health insurance companies may be restricted from making
decisions based on genetic data, but other important services such as long-term
disability, life insurance, or home loans could potentially use that data to block
individuals. Advertising and product purchases could potentially also be linked to
genetic data, as the startup Miinome has attempted to do.58
These concerns exist as concerns because of a market logic of competition that
seeks to maximize the benefit of a corporation or individual at the expense of another.
* This number is not particularly large considering that OpenSNP allows for data from 23andme,
deCODEme, and FamilyTreeDNA and that 23andme alone has genotyped over one million people.

181
It also contains the type of humanist logic discussed in chapter one that sets up a
standard for what can be considered “human” and then excludes individuals who do
not fall within those parameters. For example, a company can minimize risk by
denying a person a long-term loan if their genetic data indicated a high chance of a
fatal or debilitating illness that shows up early in life, potentially keeping the person
from paying back the loan. Or, in a Minority Report-esque situation, individuals with
genetic markers indicating aggression or certain tendencies aligned with criminal
misconduct could be incarcerated before committing any actual crime. As has been the
case with gender, race, mental illness, and other traits that differ from the medically
sanctioned norm, genetic markers could be used to classify a person as non-human if
their genetic data was made public.
Currently, these issues are hypothetical. There has been no widespread use of
genetic data to exclude or include people from a group or a major breach of ethical
use of the data, though there is a precedent in instances such as US health insurance
companies that deny coverage based on pre-existing conditions. Miinome, one of the
few companies with an explicit mission statement toward using genetic data in a
questionably commercialized way, has stalled and they have updated their outreach
efforts very little over the past two years. However, the benefits from sharing data
have made some progress. OpenSNP, Genomera, Snpedia, and Promethease all
provide more information about genetic data to their users soon after the data is
uploaded, even though very few of the open sourced studies using the information
However, the number is significant considering that this service is not highly publicized and that it is

182
have made headway. With this imbalance of hypothetical (yet very serious) risks
opposed to actual insight into one’s own genomic information, it is possible to see
how some users are not only less concerned with being excluded from institutional
operations because they lack some aspect of being “human,” but also expect the data
to be used only in non-harmful ways. Some have called for a “Hippocratic oath” for
people accessing genetic data where it is used only with good intentions. Such a call
points to an underlying assumption of shared obligation whereby users put themselves
at risk with the assumption that others will not misuse sensitive information. The
sense of justice and equality that disappears in Brown’s account of homo oeconomicus
makes a reappearance in these social media services, even though it does not
necessarily translate to the political sphere.
In order to make this move toward a logic of obligation, the underlying idea of
the human has to be radically shifted as well. Brown claims a loss of humanism
because the human becomes capital, but the way that 23andme and genetic data-
sharing services allow users to take control of their data demonstrates a refiguring of
humanism by replacing “the human” with a single, self-critical individual.*59 Users
assemble their own set of knowledge about their genetic data from assessments by
companies like 23andme along with governmental and medical sources and then share
their own data and findings with others with the intent of helping. This changes the
goal of self-care from concordance with treatment protocols (as outlined in chapter
growing.
*
This process occurs parallel to 23andme’s selling of genetic data to research companies, which is more
aligned with more traditional clinical medicine that seeks to understand disease in general.

183
two) and instead becomes a unique course of action based on the user’s unique
makeup (as in the QS projects of chapter three). Institutions like 23andme and the
FDA have reconfigured themselves to work within this shift by acting as providers of
information and protectors of the users, even if the institutions differ on how that
protection should be enacted.
On the one hand, this brings the human back into the equation, centering
treatment around the body and the existence of a person behind the data. The patient
becomes the focus instead of the disease and issues of ethical responsibility to oneself
and the larger community that can benefit from access to open source genetic data
come to the forefront. Yet, at the same time, this human is not necessarily the same
normalized construct that exists in the 19th century conception of Man outlined by
Foucault. As 23andMe’s larger project based around gathering information and
adjusting correlations between SNPs and certain traits shows, what is “normal”
becomes fluid and changeable depending on the data. Moreover, the results of the tests
are presented as chances of manifesting a certain trait or disease, not as inevitabilities.
If a 23andMe user’s genetic data shows that they should have brown eyes but they
have green eyes, the data is shown to be wrong and the user is not labeled an anomaly.
The patient in personalized genetic testing is, like in many theories of
posthumanism, an entity but not the central one. As critics of 23andMe are quick to
point out, genetic data is faulty not just because the studies are often shaky, but
because there are many other factors that go into the expression of certain traits. As
noted, these include environmental factors as well as hereditary data and even some

184
unknown aspects of how genes work. The individual here is not cut off from context
but a rallying point for all of these different factors.
Personalized genome testing also presents a move toward the body, but the
body as part data and part lived experience. The basic premise of 23andMe and similar
companies is that SNPs can be decoded into pure information to give a type of map
for various aspects of a person’s body. As in Hayles’ version of posthumanism, the
individual becomes synonymous with data that can be moved, interpreted, and copied.
Yet at the same time, personal genomics testing requires the extra step of embedding
that data back onto the life of an individual to test its accuracy, linking the data with a
singular body and precluding the possibility of downloading that data into another,
identical body as in AI.
As personal genomics shows, when posthumanism comes into contact with
medicine the result does not become a wholesale rejection of the human, a disposal of
the body, or a clean extension of medico-administrative methods of control into daily
life. Nor does it result in individuals becoming engaged in a zero sum competition
where they try to maximize their own position. Instead, it is possible to see a way
where the individual becomes reconfigured as capital through the genetic information,
but operates with an obligation to help others, even though that action may place the
individual at risk. Such an act displays the qualities of justice and equality that Brown
worries have disappeared within a society functioning according to neoliberal
principles of open markets. As demonstrated by the open source communities that
share genetic data, some individuals using these services believe that their information

185
will not be used incorrectly and can help others who are suffering from conditions that
can be treated with a larger pool of genetic data for research.
Though Brown calls for a renewed engagement with the political sphere, she
also claims that it is not democracy itself that encourages equality, justice, and
critique, but rather an ethos that can be found within democracy. Such an ethos can be
found in the individuals creating databases of genetic data, but it occurs outside of the
political. They do not engage with governmental organizations or seek to change
policy, though they generally support the de-regulation of services like 23andme so
that, theoretically, more data can be accessible to more people. These open source
databases operate within a deregulated marketplace with the belief that increasing
one’s capital does not have to be a zero sum game based on competition, but has the
potential to be a mutually beneficial activity.
1
"OpenSNP." Web. <https://opensnp.org/>.
2
Popper, Ben. The Verge. August, 2012. Print. <http://www.theverge.com/2012/8/8/3177438/cyborg-
america-biohackers-grinders-body-hackers>.
3
Gutierrez, Alberto. "23andMe, Inc. 11/22/13 Warning Letter." U.S. Food and Drug Administration.
Web. <http://www.fda.gov/ICECI/EnforcementActions/WarningLetters/2013/ucm376296.htm>.
4
Brown, Wendy. Undoing the Demos. N.p.: Duke Univ Press, 2015. 31
5
Brown 43
6
Brown 208
7
Macarthur, Daniel. "The Diversification of Consumer Genomics." Wired. Web.
<http://www.wired.com/2009/01/the-diversification-of-consumer-genomics/>.
8
Vorhaus, Dan. "Genetic Testing Service DeCODEme Shutting Down in Wake of Amgen/deCODE
Deal." Genetic Literacy Project. Web. <http://geneticliteracyproject.org/2012/12/13/genetic-testing-
service-decodeme-shutting-down-in-wake-of-amgendecode-deal/>.
9
Macarthur and Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000. Welcome to the Age
of Genomics." Wired 17 Nov. 2007 for info on how Navigenics positions itself differently than
23andMe
10
"Navigenics." Web. <https://www.navigenics.com/>.
11
"Knome | the Human Genome Interpretation Company." Web. <http://www.knome.com/>.
12
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000” 9.
13
"Health Risks." 23andme. Web. <https://www.23andme.com/you/health/risk/> and "Inherited
Conditions." 23andme. Web. <https://www.23andme.com/you/health/carrier/>.
14
Brown 31
186
15
Brown 31
16
Brown 32-33. Note that she traces a lineage of homo oeconomicus from Adam Smith to Jeremy
Bentham to Foucault. Her main modification is that homo oeconomicus focuses on investment rather
than entrepreneurialism, i.e. focusing on putting work on oneself now for future gain rather than
producing things or engaging in labor.
17
Brown 33
18
Brown 34
19
Brown 37
20
Hansen, Darah. "5Q: Anne Wojcicki, CEO 23andMe on Knowing Your DNA Data (and Being
Married to the Boss of Google)." Yahoo! Finance. Web. <https://ca.finance.yahoo.com/news/5q--anne-
wojcicki--ceo-23andme-on-knowing-your-dna-data--and-being-married-to-the-boss-of-google-
203324408.html>.
Murphy, Elizabeth. "Inside 23andMe Founder Anne Wojcicki's $99 DNA Revolution." Fast Company.
Web. <http://www.fastcompany.com/3018598/for-99-this-ceo-can-tell-you-what-might-kill-you-inside-
23andme-founder-anne-wojcickis-dna-r>.
21
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000” 12-13
22
"23andme - AU, DE, FR, & EU - Research." 23andme. Web.
<https://www.23andme.com/about/factoids/>.
23
"23andme - AU, DE, FR, & EU - Research." Parkinson’s is a heavy focus for 23andMe research
because family members of some of the founders have had the disease.
24
Lenzer, Jeanne, and Shannon Brownlee. "KNOWING ME, KNOWING YOU ." BMJ 336.19 (April
19, 2008): 859
25
Brown 36
26
Brown 139
27
Brown 141
28
Brown 136
29
Brown 140
30
Brown 139
31
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000” 11
32
Schwartz.pdf @ 27
33
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000” 11
34
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000” 11
35
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000” 11. It’s worth noting that the exact
process 23andMe uses isn’t available for review and much of the literature on how 23andMe makes
decisions or creates its algorithm may no longer be applicable, as changes in field come about quickly.
36
Parthasarathy, Shobita. "Assessing the Social Impact of Direct-to-consumer Genetic Testing:
Understanding Sociotechnical Architectures ." Genetics IN Medicine 12.9 (September, 2010): 545
37
Annas, George. "23andMe and the FDA ." The New England Journal of Medicine 370.11 (March 13,
2014): 986
38
Ramani, Donato, and Chiara Saviane. "Genetic Tests: Between Risks and Opportunities." European
Molecular Biology Organization Reports 11.12 (2010): 911
39
Kant, Immanuel. "What Is Enlightenment." www.columbia.edu. Web. 13 May 2016.
<http://www.columbia.edu/acis/ets/CCREAD/etscc/kant.html>. For a more in-depth discussion of this
and Foucault’s take on it, see previous chapters.
40
For an extensive list, see Bettinger, Blaine. "What Else Can I Do with My DNA Test Results?" The
Genetic Genealogist. Web. <http://thegeneticgenealogist.com/2013/09/22/what-else-can-i-do-with-my-
dna-test-results/>.
187
41
"23andMe Genetic Service Now Fully Accessible to Customers in New York and Maryland."
23andme. Web. <http://mediacenter.23andme.com/blog/23andme-genetic-service-now-fully-accessible-
to-customers-in-new-york-and-maryland/>.
42
"What We Do." U.S. Food and Drug Administration. Web.
<http://www.fda.gov/AboutFDA/WhatWeDo/default.htm>.
43
"23andMe Genetic Service Now Fully Accessible to Customers in New York and Maryland."
"23andMe Launches New Customer Experience – Reports Include Carrier Status That Meet FDA
Standards, Wellness, Traits, and Ancestry." 23andme. Web.
<http://mediacenter.23andme.com/blog/new-23andme/>.
44
Armstrong, David. "The Rise of Surveillance Medicine." Sociology of Health and Illness 17.3 (1995):
395
45
Foucault Birth of the Clinic 29
46
Bandelt, Hans-Jurgen, Yong-gang Yao, Martin Richards, and Antonio Salas. "The Brave New Era of
Human Genetic Testing ." BioEssays 30.11-12 (2008): 1250
47
Brown 39
48
Brown 41-42.
49
Brown 42
50
Brown 152-53
51
Brown 153-54
52
Brown 159-60
53
Brown 160
54
FDA Letter
55
Bonetta, Laura. "Getting Up Close and Personal with Your Genome ." Cell 133 (May 30, 2008): 755
56
OpenSNP,
"DIYgenomics." Web. < http://www.diygenomics.org/>.
"Personal Genome Project: Harvard." Web. <http://www.personalgenomes.org/harvard>.
"SNPedia." Web. <http://www.snpedia.com/>
57
SNPedia
58
"Miinome - It's in Your DNA." Web. <miinome.com>. It is important to note that the startup has
largely been quiet for the past few years. Their social media pages have not been updated in at least
twelve months.
59
Brown 42

CONCLUSION
This dissertation started with a warning about the dangers of the figure of the
human as well as a promise about the ethical possibilities that it could create. In these
final pages of the dissertation, it is necessary to step back and see how the health
tracking technologies that have been analyzed navigate this space between danger and
promise. The danger posed by the figure of the human comes by identifying a single
model of the human, as in Cartesian humanism. By isolating a set of characteristics, it
was believed that we could improve ourselves by amplifying particular parts that were
beneficial. These characteristics generally matched up to a Western, white, and male
figure that did not allow for any alternative forms of legitimate humans. This model of
the human carries with it a tendency toward exclusion and disempowerment that has
taken multiple forms. Colonialism and racism identified the non-European individual
as a lower, less human form of being, justifying the invasion and subjugation of entire
non-Western civilizations. Gender has been similarly configured, as the initial figure
of the human was configured along male/female lines. The female figure was
positioned as a less rational, weaker gender, which provided a reason to relegate them
to the domestic sphere. Genders outside of the male/female binary were completely
covered over and excluded from public life within this model. Within the medical
field, unhealthy individuals, especially those who were “mad” and lacked reason, were
criminalized for many years and placed in prison instead of given treatment. This is
not an exhaustive list, but some of the major areas that have been targeted by critical
theorists in recent years.
188

189
But, the other side of the human is a promise of better things to come. The
promise of the human is one of Enlightenment ideals: justice, ethics, and constant
critique of self and institution that keeps oppressive power structures at bay –
ironically some of those same power structures that are built on the humanist project
itself. Critical posthumanists see these as currently in a state of flux, goals that fail to
come to fruition with the initial Cartesian humanist project, but still not quite realized
with posthumanist critiques that scrutinize the human. Likewise, Wendy Brown has
identified these as principles very much in danger at the turn of the twenty first
century as neoliberal logic begins to take hold and direct our everyday lives. Justice,
ethics, and critique remain principles to strive toward, though newer technologies
have changed the way that they function in relation to the human. Kant’s call to use
one’s own reason as the path to ethical engagement with the world seem less relevant
in a posthumanist world operating on principles of biopower. Being self-sufficient is
no longer as clear-cut as just forming one’s own opinions, but instead involves a
complex interaction between institutionally-formed knowledges and a particular style
of enacting those knowledges in everyday, embodied life. As Brown points out,
individualism often ends up being less about creating one’s own opinions and more
about internalizing neoliberal methods of population control. Health tracking
technologies provide a salient example of how these forces play out, as they are used
for promoting one’s own health and the health of others through a critical examination
of the body, but still require interaction with and internalization of institutional
knowledge.

190
I have positioned posthumanism as a way of moving between these two poles,
trying to keep the promise of the human alive while mitigating as much of the
dangerous, normate models of the human like gender, race, healthy bodies, etc. as
possible. Criticism of posthumanism that it does not completely get beyond the human
seems to miss much of the point of posthumanist critique. Posthumanists claim that
the figure of the human is deeply problematic, but only because it is claimed as the
only type of legitimate subjectivity. As the only type of viable subject, the figure of
the human can then be used as a justification for exclusion and processes of de-
legitimation that pose the serious threat to identity politics and Enlightenment values.
Critical posthumanism teaches us not to attack or valorize the human itself but look to
the ways that the figure is used by institutions to justify the exclusion of particular
individuals and to think of alternative ways of positioning the human – namely
decentering it in favor of an embodied way of looking at the world that includes
objects and environmental factors as important actors. The question of critical
posthumanism becomes: how do or how can we understand the human without
reinscribing humanism?
One of the most important spaces where this tension plays out is in the
medical field, one of the original institutional legitimators of humanism.
Contemporary health tracking technologies illustrate a crucial area in which the
balance between the dangers of exclusionary identity politics and the promise of
ethics, justice, and critique is being reformed. Fitbit, MyFitnessPal, beddit, ResMed’s
S+, and other devices that track bodily activities aim to help users become healthier
according to a certain

191
clinical medical model of what a healthy human looks like. Users can set goals for
number of steps taken in a day or hours slept and get recommendations on how to
bring that more in line with the ideal. The intended use of these products is, on the
surface, very much a reinscription of a universal human figure. The apparent
objectivity of the recommended number of steps, calories consumed, or hours of sleep
attached to that figure ostensibly treat racial, gender, ethnic, and situational
differences as inconsequential. Moreover, the Big Data component of these
technologies has the potential to insert clinical medicine into even more aspects of
everyday life. With more data on more people and more health-related processes,
medicine could integrate itself into previously untouched aspects of life. Yet, groups
like Quantified Self work concurrently to disrupt the ability of these technologies to
create a unified idea of the human. The n=1 slogan of Quantified Self creates a space
where the figure of the human can be a singular entity with its own set of
characteristics, legitimized by medical knowledge and brought back into the sphere of
political and social participation. Unlike the human figure within humanism, this
individual is expected to differ from the normate model of the human. There is no
ideal or universal human that provides a basis for whether or not the Quantified Self
individual can engage with political and social life, creating the potential to allow
previously excluded identities to gain legitimacy within the public sphere. Moreover,
by removing the normate human as a starting point, previously unknown identities can
emerge. This figure is a type of human that follows the posthumanist model of an
embodied and fluid subject without also completely discarding the figure of the
human.

192
This dissertation has shown that contemporary medical technologies not only
deal with the opposing dangers and promises of humanism, but they also bring out the
inherent qualities within humanism that create this tension in the first place.
Humanism upholds individuality, a trait that manifests itself in a neoliberal society as
each citizen takes on more responsibility for their own self-care. But, as Chapter 2
points out, this shift in care to the patient opens up a space for alternative forms of
knowledge production. As tracking technologies become more ubiquitous in the lives
of patients, they begin to make decisions – both good and bad – that are based on their
own research and conclusions, not necessarily the orders of doctors. With regard to the
overarching ethical issues surrounding humanism, these types of decisions can be
liberating, but they also carry with them the risk of care that actually does decrease the
health of the patient. As the patient begins to take on responsibility not just for
enacting a clinically-recommended regime of self-care, but in initially creating that
regime, they also take on the responsibility for making poor decisions about their
health. Medical professionals are still obliged to help fix these issues, but not
ultimately responsible for the final outcome. The clinical and laboratory models of
medicine may devalue the actual person as they create large bodies of knowledge
about diseases in general, but they have also resulted in a great quality of life for many
individuals. Examples of this increase in quality of life discussed earlier include the
discovery and proliferation of insulin. Awareness of diabetes has been around for
many centuries, yet there was little that could be done to manage it. Laboratory
medicine in the early twentieth century discovered its relation to insulin and then

193
found a way to isolate insulin, providing a way for patients to manage their disease.
Continued laboratory research developed cheaper, synthetic insulin, which in turn
allowed an affordable and accessible way for management of the disease. Here,
laboratory medicine may not have completely taken into account the unique,
embodied situation of the patient, but was still able to come up with a way to control
a disease that had not previously been manageable.
More than just create new knowledges, self-tracking and self-care procedures
that occur outside the clinic and hospital walls significantly reorganize how power
operates. Quantified Self projects engage in a type of biopower that limits its scope to
the individual. By narrowing the focus to construct a coherent model of a single
individual throughout time rather than a cross-section of a population at a particular
moment in time, these projects take techniques of power used to legitimize an over-
arching, normate model of the human and reduce it to a legitimization of multiple,
unique human models. These are not just new knowledges for their own sake; they are
knowledges that move from the macro to the micro and facilitate an integration of
temporality into how the human is constructed. A constantly shifting and individual
figure of the human emerges alongside the posthuman hope of multiple recognized
identities. The human begins to account for varied iterations that go beyond the white,
male, Western, rational human while also allowing an individual to shift that identity
over time and different contexts. This is a type of anti-anthropocentrism akin to what I
identified in Chapter 1 as a crucial part of critical posthumanism. The move against
the figure of man here is not an outright rejection, but a move away from the human
as

194
an abstract or universal figure that can be used to exclude or disempower individuals.
But discarding the figure of the human in favor of this particular type of anti-
anthropocentrism also holds the danger of losing types of collective identity. Stable,
pre-existing identity is not always the root of oppressive power structures, as
excluding some people also means including others. Ethnicity, for example, brings
particular groups of people together in ways that provide a social safety net and a
shared culture. If the scope of the human is reduced entirely to the individual, how do
groups of people share in and create a single identity? Nationalism, culture, and
ethnicity become more difficult to imagine in a world where the guidelines of self-care
practices come from one’s own research and conclusions and instability is built-in to
the process of identity creation through constant critique.
Related to this is a question that the final chapter has attempted to deal with: is
it possible to have an ethical relation through self-tracking projects that are not just
localized in nature, but also require translating the individual into measurable
quantities? Quantified Self projects and related technologies like 23andme function by
collecting data about individuals and turning them into numbers, charts, and graphs
(often by selling it). On the one hand, as non-human ontologies like Object Oriented
Ontology and Speculative Realism address, this creates an opportunity for insights
about an individual that would not otherwise be knowable to the human. A Fitbit, for
example, has its own ontology that allows it to relate the movement of the human
body to the ground and to energy expenditure.1 Likewise, productivity-tracking apps
like RescueTime record how long certain computer programs are used, providing data

195
that can be interpreted and overlayed on top of other situational data (where the person
is, how they were feeling that day, etc.) to come to conclusions about how someone
works. This type of data is a numerical version of an individual’s actions or
situatedness within an environment. And, they allow for the creation of a unique
model of a human, while also providing a measurable way to increase or decrease a
particular force in someone’s life. A person can lose weight by using a Fitbit to make
sure they expend more energy in a day than they consume. Or, they could use
RescueTime to increase hours spent on a task or to find the optimal number of
productive hours in a day.
But, as Wendy Brown claims, this also can potentially be a dangerous
extension of neoliberal logic that could obscure human relatedness and sense of
mutual responsibility by changing them into measurable quantities rather than
approaching them through engaged, critical discussion within the demos. 23andme is
a prime example of opposing positions of life quantification. The actual business of
23andme survives by selling kits as well as renting out its databases for research and
doing their own research. People do not pay for a private screening of their DNA so
much as they pay for some information and then inclusion in further money-making
opportunities for 23andme itself. There is, again, the promise of cures for diseases and
increased information about what SNPs are tried to different traits. But, there is also
the danger of genetic information that can be tied to individuals falling into the wrong
hands that can use it to exclude the 23andme users from jobs, insurance, or social
spheres. I pointed to a community of individuals with genetic data who believe in

196
open source data and share their genetic information online for others to use. This does
show the possibility for a public sphere of information sharing and research into
genetic conditions that is not done for immediate, individual capital gains. Yet, it also
retains the danger of information mis-use, as well as the potential of undercutting the
main revenue stream for companies like 23andme. If users provide their own data for
free online, there is little reason for companies to rent out the 23andme database. Loss
of significant income could cause 23andme to shut down, removing the ability to get
the genetic data to these users in the first place.
Brown’s observation that the principles of caring for one’s fellow humans and
engaging in political critique that limits institutional power are not built in to any one
system is a salient point. These principles are advanced by a certain ethos that
expresses itself (or doesn’t). Because of this fact, it is important to pay attention to
how a system of governmentality is enacted, not necessarily focus on creating a better
system. This claim holds especially true with the technologies presented in this
dissertation, many of which are recently developed and recently available on the
market. In an appropriately neoliberal way, they have few governmental restrictions
on them and there is no clear way to regulate them, as the case of 23andme shows.
Because of the open-ended ability to use these technologies, the danger of lapsing into
using these technologies to reinforce a neoliberal logic is especially concerning.
However, the open-endedness also brings forth a spirit of critique, as people learn how
to use the technologies. Such a spirit of critique has the potential to oppose neoliberal

197
logic, as long as it is not lost through an institutionalization and corporatization of
these technologies.
One of the major underlying currents of the Quantified Self movement is a
penchant for having the latest gadgets and figuring out how to use them or using
modular devices like Arduinos and Raspberry Pis to measure a part of one’s life.
Embedded within this hacker mentality is also an excitement of new discoveries and
the desire to share with others through open source channels. Just as with democracy,
these elements of critique and desire to help others by sharing one’s own insights
about health are not built in to the technology itself. The same logic that encourages
individuals to put together their own devices or self-care plans is the same logic that
privileges individual advancement over collective advancement. In the projects of
Quantified Self and the communities sharing genetic data, the promise of a re-
invigoration of ethics, justice, and critique seem to be at the forefront, but the danger
of lapsing into individual self-interest is always lurking.
As these technologies develop, it will be necessary to continue to critique how
they relate to our notions of the human. I have identified a current tendency toward the
posthumanist promise of the human as a malleable figure central to ethics. New
technologies and their use in Quantified Self projects allow for situated, temporal self-
care regimes for individual people, but they could just as easily be used as a basis to
bring about a return to the normate, humanist idea of the human. 23andme is already
doing this with their large databases of genetic data that advance a laboratory model of
medical research. Fitbit is moving toward this as well, holding much of their activity,

198
heart rate, and geolocation data behind restrictive APIs that do not integrate with other
popular health tracking services like Apple Health. Large companies like Under
Armor are getting into the health tracking game as well, buying up services like My
Fitness Pal that holds a database of people’s meals and food intake. If kept open, these
services could provide a service to individuals and radically restructure how medicine
conceived of the human and its place within the world. Fitbit data, for example could
be used to identify irregular heartbeats that predict heart conditions. MyFitnessPal
data could be exported and tied to other biometric data like heart rate, blood pressure,
or sleep to identify how particular foods or eating patterns affect health markers. Or,
by integrating biometric data with location data from apps like Move that trace
everywhere a person goes, it would be possible to identify how the surrounding
environment affected well being. Conclusions could include whether or not a
particular city encourages a person to walk more. Or, if a large number of people in an
area began to have blood pressure or heart issues suddenly, it could be possible to
identify a chemical spill or changing air quality issues. But if kept closed, these
services could fail to provide any real benefit toward the larger health industry.
Keeping data closed prevents it from being re-contextualized, processed, and
combined with other data in unique ways. Without the ability to perform these tasks,
data stays behind proprietary software and is reduced to the uses approved by the
company that owns it.
The purpose of this dissertation has not been to identify a new form of the
human so much as argue for a way of attending to the human that can encourage

199
relations between the self and others based on individual circumstance, rather than
how well the individual fits within the normate human model. Legitimizing multiple,
shifting identities through medical discourse encourages individuals to take other
individuals on their own terms, while also requiring institutionalized recommendations
of self-care to take into account an individual’s unique, embodied circumstance. This
model also does not seek to contain the human within an identifiable set of
characteristics, but assumes it to be a process of development that always critiques and
exceeds itself. Self-tracking technologies may be the primary site that this focus on the
human occurs, but these technologies are entwined with the governmental, medical,
and corporate interests that will affect how the use of the human is developed in
coming years. Making sure that governmental, medical, and corporate institutions stay
open to models other than the traditional, humanist human remains vitally important,
especially at points of emergence and integration of those technologies like we are
experiencing now.

WORKS CITED
"23andme - AU, DE, FR, & EU - Research." 23andme. Web.
<https://www.23andme.com/about/factoids/>.
"23andMe Genetic Service Now Fully Accessible to Customers in New York and
Maryland." 23andme. Web. <http://mediacenter.23andme.com/blog/23andme-
genetic-service-now-fully-accessible-to-customers-in-new-york-and-
maryland/>.
"23andMe Launches New Customer Experience – Reports Include Carrier Status That
Meet FDA Standards, Wellness, Traits, and Ancestry." 23andme. Web.
<http://mediacenter.23andme.com/blog/new-23andme/>.
A Year in Diabetes Data | Becoming Databetic. databetic.com. Web. 15 Jul. 2014.
<http://databetic.com/?p=304>.
Anderson, Barbara, Joyce Ho, Dianne Finkelstein, and Lori Laffel. "Parental
Involvement in Diabetes Management Tasks: Relationships to Blood Glucose
Monitoring Adherence and Metabolic Control in Young Adolescents with
Insulin-dependent Diabetes Mellitus." The Journal of Pediatrics 130.2
(February, 1997): 257-265. Print.
Anderson, Ian. "Bodies, Disease and the Problem of Foucault." Social Analysis: The
International Journal of Social and Cultural Practice 37 (April, 1995): 67-81.
Print.
Anderson, Nicole. "(Auto)Immunity: The Deconstruction and Politics of ‘Bio-art’ and
Criticism." Parallax 16.4 (November, 2010): 101-116. CrossRef.
Angell, Marcia. "Caring for Women's Health -- What Is the Problem?" The New
England Journal of Medicine 329 (July 22, 1993): 271-272. Print.
Annas, George. "23andMe and the FDA ." The New England Journal of Medicine
370.11 (March 13, 2014): 985-988. Print.
Armstrong, David. "The Rise of Surveillance Medicine." Sociology of Health and
Illness 17.3 (1995): 393-403. Print.
Badmington, Neil. Posthumanism. N.p.: Palgrave Macmillan, 2000.
Bandelt, Hans-Jurgen, Yong-gang Yao, Martin Richards, and Antonio Salas. "The
Brave New Era of Human Genetic Testing ." BioEssays 30.11-12 (2008):
1246-1251. Print.
200

201
Barooah, Robin. The False God of Coffee | Quantified SelfQuantified Self.
quantifiedself.com. Web. 14 Feb. 2013.
<http://quantifiedself.com/2009/10/the-false-god-of-coffee/>.
"Ben Finn: Improving My Sleep." Quantified Self. Web.
<http://quantifiedself.com/2014/11/ben-finn-improving-sleep/>.
Bettinger, Blaine. "What Else Can I Do with My DNA Test Results?" The Genetic
Genealogist. Web. <http://thegeneticgenealogist.com/2013/09/22/what-else-
can-i-do-with-my-dna-test-results/>.
Bissell, Paul, Carl May, and Peter Noyce. "From Compliance to Concordance:
Barriers to Accomplishing a Re-framed Model of Health Care Interactions."
Social Science & Medicine 58 (2004): 851-862. Print.
Bogost, Ian. Alien Phenomenology, or What It's Like to Be a Thing. N.p.: U of
Minnesota Press, 2012.
Bonetta, Laura. "Getting Up Close and Personal with Your Genome ." Cell 133 (May
30, 2008): 753-756. Print.
Borus, Joshua, and Lori Laffel. "Adherence Challenges in the Management of Type 1
Diabetes in Adolescents: Prevention and Intervention." Curr Opin Pediatr 22.4
(August, 2010): 405-411. Print.
Bowden, Mark. "The Measured Man." The Atlantic. Web.
<http://www.theatlantic.com/magazine/archive/2012/07/the-measured-
man/309018/>.
---. The Measured Man - Mark Bowden - the Atlantic. www.theatlantic.com. Web. 13
Feb. 2013. <http://www.theatlantic.com/magazine/archive/2012/07/the-
measured-man/309018/?single_page=true>.
Brok-Kristensen, Mikkel. "Changing Diabetes Care for Good." EPIC (2007): 91-103.
Print.
Brown, Wendy. Undoing the Demos. Duke Univ Press, 2015.
Bryant, Levi. "Worries About OOO and Politics." Larval Subjects .
larvalsubjects.wordpress.com. Web. 13 May 2016.
<https://larvalsubjects.wordpress.com/2012/05/29/worries-about-ooo-and-
politics/>.
Bryant, Levi R. "The Democracy of Objects."(2011).

202
Buabeng, Kwame. "Unaffordable Drug Prices: The Major Cause of Non-compliance
with Hypertension Medication in Ghana." J Pharm Pharmeceut Sci 7.3 (2004):
350-352. Print.
Buston, Katie, and Stuart Wood. "Non-compliance Amongst Adolescents with
Asthma: Listening to What They Tell Us About Self-management ." Family
Practice 17.2 (2000): 134-138. Print.
Campbell, R, M Evans, M Tucker, B Quilty, P Dieppe, and J.L. Donovan. "Why Don't
Patients Do Their Exercises? Understanding Non-compliance with
Physiotherapy in Patients with Osteoarthritis of the Knee." J Epidemio
Community Health 55 (2001): 132-138. Print.
Castree, Noel, Catherine Nash, Neil Badmington, Bruce Braun, Jonathon Murdoch,
and Sarah Whatmore. "Mapping Posthumanism: An Exchange." Environment
and Planning A 36.8 (2004): 1341-1363.
Chatterjee, JS. "From Compliance to Concordance in Diabetes." J Med Ethics 32
(2006): 507-510. Print.
"Christel De Maeyer: My Journey with Sleep Monitoring." Quantified Self. Web.
<http://quantifiedself.com/2014/09/christel-de-maeyer-journey-sleep-
monitoring/>.
Claydon, Bridget, and Nathan Efron. "Non-compliance in General Health Care ."
Opthal. Physiol. Opt. 14 (July, 1994): 257-264. Print.
Cockburn, Jill, Robert Gibberd, Alexander Reid, and Robert Sanson-Fisher.
"Determinants of Non-compliance with Short Term Antibiotic Regimens ."
British Medical Journal 295 (October 3, 1987): 814-817. Print.
Conrad, Peter. "The Meaning of Medications: Another Look at Compliance." Soc Sci
Med 20.1 (1985): 29-37. Print.
"David Joerg: Building My Personal Operating System." Quantified Self. Web.
<http://quantifiedself.com/2014/12/david-joerg-building-personal-operating-
system/>.
Davies, Tony. Humanism. London ; New York: Routledge, 2008.
Davis, Matthew R. "Biomedical Control and Diabetes Care." Science as Culture 7.1
(March, 1998): 69-93.
"DCCT and EDIC: The Diabetes Control and Complications Trial and Follow-up
Study." National Diabetes Information Clearinghouse Print.
<http://www.niddk.nih.gov/about-niddk/research-areas/diabetes/dcct-edic-

203
diabetes-control-complications-trial-follow-up-study/Documents/DCCT-
EDIC_508.pdf>
Derrida, Jacques. "The Ends of Man." Philosophy and Phenomenological Research
30.1 (September, 1969): 31-57. Print.
Descartes, René. Key Philosophical Writings. Hertfordshire: Wordsworth Editions
Limited, 1997.
"Diabetes and Hypoglycemia." Diabetes.co.uk. Web.
<http://www.diabetes.co.uk/Diabetes-and-Hypoglycaemia.html>.
"Diabetes A-Z." National Institute of Diabetes and Digestive and Kidney Diseases.
Web. <http://diabetes.niddk.nih.gov/dm/pubs/overview/index.aspx#managed>.
Dimatteo, Robin. "Depression Is a Risk Factor for Noncompliance with Medical
Treatment." Arch Intern Med 160 (July 24, 2000): 2101-2107. Print.
"Diseases and Conditions: Diabetes." Mayo Clinic. Web.
<http://www.mayoclinic.org/diseases-
conditions/diabetes/basics/definition/con-20033091>.
"DIYgenomics." Web. < http://www.diygenomics.org/>.
Doug Kanter - A Year of Diabetes Data on Vimeo. vimeo.com. Web. 14 Jul. 2014.
<http://vimeo.com/79837532>.
Duhaime-Ross, Arielle. "23andMe Plans to Move Beyond Genetic Testing to Making
Drugs." The Verge. Web.
<http://www.theverge.com/2015/3/12/8199303/23andme-drug-development-
testing>.
"The Effects of Insulin on the Body." Healthline. Web. <
http://www.healthline.com/health/diabetes/insulin-effects-on-body>.
Ferzacca, Steve. ""Actually, I Don't Feel That Bad": Managing Diabetes and the
Clinical Encounter." Medical Anthropology Quarterly 14.1 (2000): 28-50.
Print.
Fitbit. www.fitbit.com. Web. 19 Feb. 2013. <http://www.fitbit.com/>.
Forbes, John. The Cyclopaedia of Practical Medicine. Vol. 4. N.p.: Blanchard and
Lea, 1854.

204
Foucault, Michel. "Abnormal: Lectures at the Collège De France, 1974-1975, Edited
by Valerio Marchetti & Antonella Salomoni, Translated by Graham Burchell."
New York: Picador (2003).
---. The Birth of the Clinic; An Archaeology of Medical Perception. N.p.: New York,
Pantheon Books, 1973. Print.
---. "The Hermeneutics of the Subject." Lectures at the Collège de France, 1981-1982
(2005).
---. The History of Sexuality. N.p.: New York, Pantheon Books, 1978. Print.
---. The Order of Things : An Archaeology of the Human Sciences. New York: Vintage
Books, 1994.
---. "What Is Enlightenment." Ethics, Subjectivity and Truth. Ed. Paul Rabinow. Trans.
Robert Hurley. New York: The New Press, 1994. 303-320. Print.
Fox, Susannah. "Visualize This: An E-Patient’s Medical Life History." E-patients.net.
Web. <http://e-patients.net/archives/2012/03/visualize-this-an-e-patients-
medical-life-history.html>.
Garland-Thomson, Rosemarie. "Extraordinary Bodies: Figuring Physical Disability in
American Literature and Culture." New York: Columbia UP (1997).
Gary Wolf: The Quantified Self | Video on TED.com. www.ted.com. Web. 5 Feb. 2013.
<http://www.ted.com/talks/gary_wolf_the_quantified_self.html>.
Geary, Mary Ann. "An Analysis of the Women's Health Movement and Its Impact on
the Delivery of Health Care Within the United States." Nurse Practitioner
20.11 (November, 1995): 24-35. Print
Goetz, Thomas. "23AndMe Will Decode Your DNA for $1,000. Welcome to the Age
of Genomics." Wired 17 Nov. 2007: 1-15. Print
--. "Patient Empowerment and the Traditional Medical Model: A Case of
Irreconcilable Differences?" Wired 17 Nov. 2007: n. pag. Print.
"Gordon Bell: Every Beat of My Heart." Quantified Self. Web.
<http://quantifiedself.com/2015/03/gordon-bell-every-beat-heart/.>.
Gutierrez, Alberto. "23andMe, Inc. 11/22/13 Warning Letter." U.S. Food and Drug
Administration. Web.
<http://www.fda.gov/ICECI/EnforcementActions/WarningLetters/2013/ucm37
6296.htm>.

205
Hansen, Darah. "5Q: Anne Wojcicki, CEO 23andMe on Knowing Your DNA Data
(and Being Married to the Boss of Google)." Yahoo! Finance. Web.
<https://ca.finance.yahoo.com/news/5q--anne-wojcicki--ceo-23andme-on-
knowing-your-dna-data--and-being-married-to-the-boss-of-google-
203324408.html>.
Halliwell, Martin, and Andy Mousley. Critical Humanisms : Humanist. Edinburgh:
Edinburgh University Press, 2003.
Haraway, Donna. Simians, Cyborgs, and Women. New York: Routledge, 1991. Print.
Haraway, Donna J. Primate Visions: Gender, Race, and Nature in the World of
Modern Science. N.p.: routledge, 2013.
Harman, Graham. "Guerilla Metaphysics." Phenomenology and the carpentry of
Things. Chicago: Open Court (2005).
Hayles, N Katherine. How We Became Posthuman: Virtual Bodies in Cybernetics,
Literature, and Informatics. N.p.: University of Chicago Press, 1999.
Haynes, Brian, Elaine Wang, and Marleide da Mota Gomes. "A Critical Review of
Interventions to Improve Compliance with Prescribed Medications." Patient
Education and Counseling 10 (1987): 155-166. Print.
"Health Risks." 23andme. Web. <https://www.23andme.com/you/health/risk/>.
Heidegger, Martin, Joan Stambaugh, and Dennis J Schmidt. Being and Time. N.p.:
SUNY Press, 2010.
History of Insulin - Discovery to Modern Day Timeline. www.diabetes.co.uk. Web. 13
May 2016. <http://www.diabetes.co.uk/insulin/history-of-insulin.html>.
Horkheimer, Max, Theodor W Adorno, and Gunzelin Schmid Noerr. Dialectic of
Enlightenment : Philosophical Fragments. Stanford, Calif.: Stanford
University Press, 2002.
"How to Track Your Sleep: Learn From Daniel Gartenberg at QS15." Web.
<http://quantifiedself.com/2014/11/qs15-conference-preview-daniel-
gartenberg-tracking-sleep/>.
"Inherited Conditions." 23andme. Web.
<https://www.23andme.com/you/health/carrier/>.
Jewson, N D. "The Disappearance of the Sick-man From Medical Cosmology, 1770-
1870." Int J Epidemiol 38.3 (June, 2009): 622-33. Print.

206
Kant, Immanuel. "What Is Enlightenment." www.columbia.edu. Web. 13 May 2016.
<http://www.columbia.edu/acis/ets/CCREAD/etscc/kant.html>.
"Knome | the Human Genome Interpretation Company." Web.
<http://www.knome.com/>.
Know Thyself: Tracking Every Facet of Life, From Sleep to Mood to Pain, 24/7/365.
www.wired.com. Web. 11 Apr. 2013.
<http://www.wired.com/medtech/health/magazine/17- 07/lbnp_knowthyself?
currentPage=all>.
"Kouris Kalligas: Analyzing My Weight and Sleep." Quantified Self. Web. <
http://quantifiedself.com/2014/09/kouris-kalligas-analyzing-weight-sleep/>.
Larry Smarr on Chron's Disease and Quantified SelfQuantified Self.
quantifiedself.com. Web. 13 Feb. 2013.
<http://quantifiedself.com/2013/02/larry_smarr_croneshope_in_data/#more-
5853>.
Lenzer, Jeanne, and Shannon Brownlee. "KNOWING ME, KNOWING YOU ." BMJ
336.19 (April 19, 2008): 858-860. Print.
Living the Quantified-Self Way: Like a Weirder, Hive-Mindier Weight Watchers |
Vanity Fair. www.vanityfair.com. Web. 11 Apr. 2013.
<http://www.vanityfair.com/culture/2013/02/quantified-self-hive-mind-weight-
watchers>.
Loree, Jewel. "Self-Quantifiers Meetup at Tableau." Quantified Self. Web.
<http://www.tableau.com/public/blog/2014/05/self-quantifiers-meetup-tableau-
2478>.
Macarthur, Daniel. "The Diversification of Consumer Genomics." Wired. Web.
<http://www.wired.com/2009/01/the-diversification-of-consumer-genomics/>.
MacCracken, Joan, Donna Hoel, and Lois Jovanovic. "From Ants to Analogues:
Puzzles and Promises in Diabetes Management." Postgraduate medicine 101.4
(1997): 138-150.
McCurdy, Kathryn. "How Visualizing Health Problems Could Help Solve
Medical Mysteries." [sensical]. Web.
<https://sensical.wordpress.com/2011/11/16/how-visualizing-health-problems-
could-help-solve-medical-mysteries/>.
The Measured Life | MIT Technology Review. www.technologyreview.com. Web. 5
Feb. 2013. <http://www.technologyreview.com/featuredstory/424390/the-
measured-life/>.

207
Miah, Andy. "Posthumanism: A Critical History." Medical Enhancements &
Posthumanity. New York: Routledge, 2007. Print.
"Miinome - It's in Your DNA." Web. <miinome.com>.
Moravec, Hans. Mind Children. N.p.: Cambridge Univ Press, 1988.
Murphy, Elizabeth. "Inside 23andMe Founder Anne Wojcicki's $99 DNA
Revolution." Fast Company. Web.
<http://www.fastcompany.com/3018598/for-99-this-ceo-can-tell-you-what-
might-kill-you-inside-23andme-founder-anne-wojcickis-dna-r>.
"Navigenics." Web. <https://www.navigenics.com/>.
"OpenSNP." Web. <https://opensnp.org/>.
"Overview." Qualcomm Tricorder XPRIZE. tricorder.xprize.org. Web. 13 May 2016.
<http://tricorder.xprize.org/about/overview>.
Parthasarathy, Shobita. "Assessing the Social Impact of Direct-to-consumer Genetic
Testing: Understanding Sociotechnical Architectures ." Genetics IN Medicine
12.9 (September, 2010): 544-547. Print.
"Patient Empowerment and the Traditional Medical Model: A Case of Irreconcilable
Differences?" Diabetes Care. care.diabetesjournals.org. Web. 13 May 2016.
<http://care.diabetesjournals.org/content/18/3/412>.
"Personal Genome Project: Harvard." Web.
<http://www.personalgenomes.org/harvard>.
Popper, Ben. The Verge. August, 2012. Print.
<http://www.theverge.com/2012/8/8/3177438/cyborg-america-biohackers-
grinders-body-hackers>.
Poretsky, Leonid. Principles of Diabetes Mellitus. N.p.: Springer, 2010.
"QS Access App." Quantified Self. Web. <http://quantifiedself.com/access-app/app>.
The Quantified Man: How An Obsolete Tech Guy Rebuilt Himself for the Future |
Wired Enterprise | Wired.com. www.wired.com. Web. 11 Apr. 2013.
<http://www.wired.com/wiredenterprise/2013/02/quantified-work/all/>.
The Quantified Self: Counting Every Moment | the Economist. www.economist.com.
Web. 5 Feb. 2013. <http://www.economist.com/node/21548493>.

208
Quantified Self How-To: Designing Self-Experiments. hplusmagazine.com. Web. 5
Feb. 2013. <http://hplusmagazine.com/2012/11/14/quantified-self-how-to-
designing-self-experiments/>.
Quantified Self | Self Knowledge Through NumbersQuantified Self | Self Knowledge
Through Numbers. quantifiedself.com. Web. 13 May 2016.
<http://quantifiedself.com/>.
Rabinow, Paul, and Nikolas Rose. "Biopower Today." BioSocieties 1 (2006): 195-217.
Print.
Ramani, Donato, and Chiara Saviane. "Genetic Tests: Between Risks and
Opportunities." European Molecular Biology Organization Reports 11.12
(2010): 910-913. Print.
Ramirez, Ernesto. QS and Mindfulness Quantified Self. quantifiedself.com. Web. 28
Feb. 2013. <http://quantifiedself.com/2013/02/qs-and-mindfulness/>.
---. "Talking Data with Your Doc : The Patient." Quantified Self. Web.
<http://quantifiedself.com/2012/03/talking-data-with-your-doc/>.
Roden, David. Posthuman Life: Philosophy at the Edge of the Human. N.p.:
Routledge, 2014.
Rose, Nikolas. The Politics of Life Itself: Biomedicine, Power, and Subjectivity in the
Twenty-first Century. N.p.: Princeton University Press, 2007.
Ross, Fiona. "Patient Compliance—Whose Responsibility?" Soc Sci Med 32.1 (1991):
89-94. Print.
Ruzek, Sheryl. "Towards a More Inclusive Model of Women's Health." American
Journal of Public Health 83.1 (January, 1993): 6-8. Print.
Scanadu | Home. www.scanadu.com. Web. 13 May 2016.
<https://www.scanadu.com/>.
Scanadu | Vitals. www.scanadu.com. Web. 13 May 2016.
<https://www.scanadu.com/products/vitals>.
Schwartz, Peter. "The Value of Information and the Ethics of Personal- Genomic
Screening ." The American Journal of Bioethics 9.4 (2009): 26-27. Print.
Sky Christopherson - Self Quantification and Performance on Vimeo. vimeo.com.
Web. 13 Feb. 2013. <http://vimeo.com/40265860>.
"Sleep Cycle." Web. <Sleepcycle.com>.

209
"Sleepio." Web. <Sleepio.com>.
"SNPedia." Web. <http://www.snpedia.com/>.
Stephen Wolfram Blog : The Personal Analytics of My Life.
blog.stephenwolfram.com. Web. 5 Feb. 2013.
<http://blog.stephenwolfram.com/2012/03/the-personal-analytics-of-my-life/>.
The ‘So What’ of the Quantified Self | TechCrunch. techcrunch.com. Web. 5 Feb.
2013. <http://techcrunch.com/2012/03/31/quantified-self-so-what/>.
"Topic Archives: Videos." Quantified Self. Web.
<http://quantifiedself.com/topics/videos/>.
Trombley, Jeremy. "Ethics and Politics: What Are You Asking?" Larval Subjects .
larvalsubjects.wordpress.com. Web. 13 May 2016.
<https://larvalsubjects.wordpress.com/2012/05/29/ethics-and-politics-what-
are-you-asking/#comment-133863>.
Trostle, James. "Medical Compliance As An Ideology." Soc Sci Med 27.12 (1988):
1299-1308. Print.
Vivienne Ming - Tracking My Son's Diabetes on Vimeo. vimeo.com. Web. 14 Jul.
2014. <http://vimeo.com/81272562>.
Vorhaus, Dan. "Genetic Testing Service DeCODEme Shutting Down in Wake of
Amgen/deCODE Deal." Genetic Literacy Project. Web.
<http://geneticliteracyproject.org/2012/12/13/genetic-testing-service-
decodeme-shutting-down-in-wake-of-amgendecode-deal/>.
"Wearable Technology - Statistics & Facts." Statista. www.statista.com. Web. 13 May
2016. <http://www.statista.com/topics/1556/wearable-technology/>.
Welcome to Zeo Sleep Manager | Zeo Sleep Manager. www.myzeo.com. Web. 16 Apr.
2013. <http://www.myzeo.com/sleep/>.
"What We Do." U.S. Food and Drug Administration. Web.
<http://www.fda.gov/AboutFDA/WhatWeDo/default.htm>.
Wolf, Gary. The Data-Driven Life - NYTimes.com. www.nytimes.com. Web. 15 Feb.
2013. <http://www.nytimes.com/2010/05/02/magazine/02self-measurement-
t.html?_r=3&pagewanted=all&>.
---. "Our Three Prime Questions." Quantified Self. Web.
<http://quantifiedself.com/2011/09/our-three-prime-questions/>.

210
---. Quantified Self | Aether. aether.com. Web. 14 Feb. 2013.
<http://aether.com/quantifiedself>.
Wolfe, Cary. "What Is Posthumanism?" Journal for Critical Animal Studies IX.1/2
(2011): 235-241. Print.

