


1
Child Mortality Rates in Africa: Exploring the Relationship between Poverty and Health
ASU
ECN 355 - Economics of Health Care
Date
Abstract (250 Words)

2
It is stated that a prosperous country is one that is healthy. However, the majority of Sub-
Saharan African (SSA) nations have poor health outcomes as a result of their poverty levels.
Poverty and health have been proven to be causally linked in both directions. Several studies
have found a relationship between poverty and health, and vice versa. However, there are few
studies in Africa that look at the relationship between poverty and poor health, and the results are
equivocal. The relationship between ill-health and poverty in Africa is investigated in this study,
which uses infant mortality rates as a proxy for health and the household income indices as a
substitute for poverty. We estimate the connection between health and poverty using data from
the WHO 2008-09 using two-stage least - square quintile regression approaches (mortality). The
findings reveal that infant mortality in Africa are influenced by, home type, mothers' education,
fresh water accessibility, sanitation, and cooking fuel, as well as the gender of the household
head. The goal of this project is to establish and execute programs and policies including
economic opportunities and parental education targeted at lowering child mortality and poverty,
especially in rural areas. Furthermore, it intends to inform African governments that they should
raise public knowledge about the need of sanitation and enhance basic health education
promotion in educational institutions. Most notably, it proposes that the authorities and other
development organizations boost the provision of clean water in rural regions and promote the
use of low-polluting fuels.
Keywords: Health, Poverty, Child Mortality, Millennium Development Goals, World Health
Organization, Sub-Saharan Africa, Empirical Data
JEL Classification: O13; O17; Q43; Q54
Child Mortality Rates in Africa: Exploring the Relationship between Poverty and Health

3
Introduction and Background (603 words)
Poverty and health are key indicators of human well-being, and their interactions are
intimately linked (Adams et al., 2003). Understanding the factors that influence health and
poverty, as well as how they change over time, has crucial policy implications. Numerous studies
have found a strong link between health and socioeconomic status (SES), which is frequently
assessed by income (Adams et al., 2003). Theoretically, there might be a positive or negative
relationship between socioeconomic level and health. On the one hand, low socioeconomic
position (for example, income poverty) can result in poor health owing to hunger and a lack of
access to healthcare. On the other side, when illness decreases one's capacity to work, it can lead
to poor income and consequently poverty
Poverty
Poverty is defined as a lack of adequate resources to sustain some normative functions
(Ravallion 2010). These include both basic survival requirements and the expenses of social
inclusion for engaging in economic and social activities (Ravallion 2010). Absolute poverty
refers to the cost of the bare essentials for human survival, whereas relative poverty refers to the
cost of the bare economic, social, political, and economic commodities necessary to maintain an
acceptable level of living in a particular community (World Bank, 2000). Food insecurity refers
to a person's inability to fulfill the minimal nutritional (calorie) needs for healthy growth as well
as human body maintenance. The amount of money needed to fulfill the suggested daily average
calorie allotment of 2,200 in accordance to the agreed-upon food basket is known as the food
poverty line. Poverty is defined as a lack of both non-food and food fundamental needs. Extreme
poverty happens when a person cannot satisfy her or his minimum calorie need even if she or he
spends all of her or his money on food (World Bank, 2000). Since colonial times, poverty has

4
become a big concern in Africa, as the number of countries have stayed relatively poor, with a
large number of unemployed and low-income individuals in their populations.
Africa's Healthcare Situation
Sub-Saharan Africa remains to have world's worst health care, with few countries capable
of spending between $35 and $40 each person for each year considered by World Health
Organization considers as the minimum for adequate treatment (World Bank, 2000).
Furthermore, despite rampant poverty, people's out-of-pocket healthcare costs accounts for half
of a region's total health spending. Significant progress has been made against HIV/AIDS,
tuberculosis, and malaria thanks to the generosity of donors. However, the bulk of the area lacks
adequate health-care infrastructure, and competent medical personnel are in short supply (World
Bank, 2000). As Africa's economies expand, the demand for better health care will only increase.
The Child Mortality Rate in Africa
Wright and Yogo (2012) says that Africa accounted for almost 14% of the global child
mortality burden in 1960. Despite having just 11% of the global population, Sub-Saharan Africa
currently accounts for more than half of all child mortality (Younger, 2011). Africa must seek to
bridge the gap as rapidly as possible if egvelopment goals are met, which is to reduce child
mortality by two-thirds, is to be realized. In 2003, the death rate for children as young of five
was 172 fatalities per 1000 live births, down from 188 in 1990. (Wolfson et al., 2010). The
Sustainable development goals ask for a 7.8% annual average rate of decline, whereas this
translates to a 9.5% total drop. A number of challenges must be overcome in order to reduce
child mortality in Africa (Wichman, 2016). Child mortality in Africa are thought to be linked to
caregivers' diminishing caring abilities, as well as increased food and poverty insecurity.

5
Review of the Literature (909 words)
Mutunga (2004) performed research on the impact of socioeconomic and environmental
factors (mother's education, source of water, cooking fuel, sanitation, and electricity on
childhood mortality at various ages. The modified health production conceptual foundation
Shultz (1984) has been used in conjunction with the hazard rate model. The findings revealed
that environmental and socio - economic factors influenced child mortality significantly.
However, the study did not look at the impact of poverty on infant mortality rates or the causal
mechanism that leads to it.
Using data from, Elmahdi (208) investigated the socioeconomic factors of child mortality
in Africa. In this study, a logistic regression analysis was used. Other than the mother's
employment and wealth indices, there was no significant relationship between other
socioeconomic characteristics and child mortality in both wealthy and poor regions, according to
the data. Breastfeeding was also shown to be the most important indicator of infant mortality,
followed by ethnicity, reproductive characteristics (birth order and interval), and gender, with
gender having the least impact. However, the study did not look at the link between Infant
mortality and poverty.
In light of Africa's poverty levels, Amina (2008) investigated the levels, trends, and
differences in childhood mortality. The Africa Comprehensive Household and Budget Study
2005/06 was used in the research. The Trussel (1974) variation of the Brass technologies were
used to calculate the likelihood of a kid dying between birth and a specific age. Child mortality
rates rose in tandem with poverty levels, according to the research. In North Northern and
Central Africa, on the other hand, non-poor families had greater mortality rates than poor
household’s health. Unlike the study discussed above, which used the Africa Comprehensive

6
Household and Expenditure Survey to investigate the association between health and poverty
using infant mortality rates as a health indicator, this study uses the Africa Demographic And
health Survey 2009/10. Amina (2008) did not look at the direction of the poverty-child mortality
link. This research also aims to determine the impact of poverty on infant mortality rates by
identifying the processes involved.
Mariara et al. (2012) looked at the factors that influence African child survival. Survival
models were employed to study child poverty, and an asset index was utilized as a measure of
well-being. The study used primary micro-level data on the Gross National Product, health
spending, and geographical levels of health services for the year of a child's birth supplemented
with Demographic health Survey from 1993 to 2003. Child survival was studied using the
proximal determinant approach. According to the study's findings, there was a substantial link
between child survival and poverty (asset index). Furthermore, children in rural areas were more
likely to be poor and, as a result, to die than their urban counterparts. The researchers did not
look at the potential of a coincidental link between child survival and poverty. This study looks
at the link between impoverishment and ill-health by using a model that allows for the evaluation
of the connection between the two, even if they are both possibly endogenous.
Ngigi (2013) investigated the factors that influence child mortality in Africa. The study
goals were met using the logit model and the Schultz (1984) framework. Mother's age, total
number of children born by a mother, family wealth, newborn birth size, mother's education, and
religion were all found to be significant factors of infant mortality. However, the study did not
look at the impact of poverty on child mortality. The model used in this study evaluates the
genuine effect of poverty on child mortality. Ahmed et al. (2012), on the other hand, looked at
the causal relationship between health and poverty in Nigeria, using HIV/AIDS as a health

7
indicator. Data from the Annual time series from 1990 to 2009 were used in the study. The
Granger causality test was used to meet the study's goals. According to the data, there was no
clear relationship between HIV and poverty in Nigeria, meaning that poverty had no impact on
the country's HIV rates. HIV, on the other hand, has been linked to an increase in poverty rates.
One criticism of the research is that it did not look at the short-term link between poverty and
HIV. This study, on the other hand, investigates the association between poverty and poor health
in Africa utilizing instrumental methodology and cross-sectional data.
Foloko (2009) used the Lesotho DHS datasets for 2004/05 to study the factors of infant
mortality rates in Lesotho. In order to analyze child mortality, the researchers used Rosenzweig
and Schultz's (1983) approach and hazard model. Household income, mother's education, and
sanitary facilities were all shown to be major drivers of child mortality. However, the study did
not look at the direct influence of poverty on infant mortality rates or the mechanism that causes
it. In Bangladesh, Gwatkin et al. (2000) investigated socioeconomic inequalities in health,
nutrition, and population. They looked at differences in baby and under-5 mortality, malnutrition
levels, diarrhea incidence, and respiratory infections using DHS data from 40 underdeveloped
nations. According to the data, a kid born in a home belonging to the poorest quintile is almost
twice as likely as a baby conceived in a household from to the highest income quintiles. Another
conclusion from the study seemed to be that nations with lower child rates of morbidity and
mortality had bigger socioeconomic inequality. The study made no effort to describe the
relationship between poverty and illness. The impact of impoverishment on child mortality is
investigated in this study.
Aims, Objectives and Research Questions
Aim of the study

8
The aim of this is to determine the impact of poverty on human health and more
specifically regarding how it influences child mortality in Africa. This study’s topic is a medical
and economics study topic. It also aims to influence the ways in which policies are formulated.
These formulated policies targeted at reducing health disparities, policymakers must understand
the magnitude of the relationship between health and poverty. Medical academics and public
health specialists believe there is a link between poverty and illness (Smith, 1999).
The other aim of this study is changing from therapies and healthcare to social and
economic factors such as income, job status, environment, and income distribution which
Wilkinson and Marmot (1998) deems very important is determining the level of poverty in a
country and consequently determining the mortality rates among children. However, economists
appear more concerned in the impact of health on socioeconomic position, notably on labor
supply and salaries.
Newborn and child mortality rates are strongly connected to incomes, but the
distributional characteristics of child mortality seem to be much more susceptible to the
wellbeing of the poor (Younger, 2011). The health of the poor is argued by Spencer (2005). The
sharp decline in income due to macroeconomic crises or other circumstances may negatively
impact health (Paxton and Shady, 2004). Therefore, with such information available in the public
domain, those concerned with public health matters will help in steering programs that will push
for the achievement of decreased poverty which have the ability to influence poverty and
mortality rates among children in Africa.
Others contend that health is not always linked to money and spending, opening the door
to studying health in connection to impoverishment (Younger, 2001). There are few research on
the link between ill-health and poverty in Africa. The effects of poverty on infant mortality rates

9
in Africa has not been extensively studied. The study investigates the relationship between infant
mortality and poverty. It is important to understand if there is a positive or negative relationship
between socioeconomic level and health.
Previous research in Africa on infant mortality and poverty used WHO data from 2003
and UNCEF data from 2007/08. For example, Amina (2008) studied child mortality trends,
patterns, and disparities in poverty. In their study, Mariara et al. Mutunga (2004) studied how
family socioeconomic and environmental factors affect baby and child mortality. These
empirical research in Africa have not examined the link between poverty and ill-health, assuming
that the relationship runs both ways. More importantly, the previous research did not fully focus
on the influence of poverty on infant mortality rates and the processes involved. This study also
aims at filling up certain information gaps that were left by other studies.
Research Objective
This study's goal is to research the link between poverty and illness in Africa. These
objectives are: t
I. To assess the impact of poverty on infant mortality rates in Africa.
II. To determine the link between poverty and child mortality in Africa
III. To make policy suggestions for addressing the health needs of Africa children.
Research Question
This study seeks to answer the questions below in the process of trying to explore the
relationship that exist between poverty and health in influencing the child mortality rates in the
continent of Africa.

10
The first, question that his study seeks to answer is:
I. How does poverty affect child mortality in Africa?
II. How strong is the relationship that exist between poverty and infant mortality in Africa?
III. What influences the relationship between poverty and child mortality in Africa?
Methodology (596 words)
Analytical Framework
Rosenzweig and Schulltz (1983) model is used as refined by Schultz (1984). The
framework's primary premise is that households devote time and resources to produce
commodities, some of which are marketed and others that are consumed at home. The utility
function U, which would be a function of the composite consumer good X, composite
environment quality Y, and H the health condition of n household children, H represents
household health choices. It is written as:
U= U(X Y H)….1
Child health is represented by a child specified health input (I), that does not impact
parental utilities directly, and infant health endowment (Rosenzweig and Schultz, 1983.
Then child health production:
H= F(Y, I, K, µ)…2
Such that
K is household's health knowledge, while Y, I, and µ remain as stated above.

11
Y is influenced by the infant's health endowment identified as (MC), household choice
(PR), market pricing, and restrictions from household's physical environment identified as (P) as
well as wealth (W).
Considering that the production function (2) and the household finances restriction, the
utility function denoted by (1) is maximized.
The household finances limitation:
PX + PY + PI = Z
Where
Z -family income.
PX - Price of consumer items with direct impact on health.
PY -price of health-related items.
PI stands for the price of a child's individual health input.
Adopting Mwabu (2008) in the maximization formula (1) according to healthcare
production function denoted as (2) as well as the budget restriction (3).
Households demand function:
Dx = D(PY, PI, K, W,µ) ...4
Dx = D(PY, PI, K, W,µ) ...4
DI = D(PY, PI, K, W,µ) ....6

12
Through the substitution of demand function (5) and (4) into the health production
function, the result obtained by Mwabu (2008) is indicated below.
H= F (DX (PY, PI , K,W ,µ), DY (PY, PI , K,W ,µ ),K, µ) … 7
H= F (PY, PI , K, W, µ) ...8
The relative prices (PI and PY), the household's health knowledge doted as (K), the
household wealth (W), and the infant's health endowments for all children (µ) may all be
described by expression (8).
The simplified input demand function become from formula (9). infant health is
described by determinative inputs to infant health (Y), infant health inputs (I), the household's
health knowledge (K), the household's wealth (W) as well as infant health endowment (µ),
(Mwabu, 2008).
Model Specification
Child mortality model:
CM= f(MED,BSIZ,G, MAGE, MREL, MMS,TNC, HHW, SCF, RT,AW, AS, PD, TTI, )........10
Where:
CM- based on the likelihood of a kid dying before their fifth birthday, with a value of (1)
if the child is believed to have died and (0) if the infant is reported alive. The variable names,
definitions, and apriori estimates of the parameters in (10)
Estimation of the Model

13
To achieve the study's goals, and in accordance with Mwabu and Ajakaiye (2009), a
structural model for quantifying the causal influence of poverty (as measured by family wealth)
on health is used. The model's formulation.
Y= ..........11
……..12
Where Y is the therapy variable and X is the health output variable (child mortality)
Gender, age, and residential location are all external control factors in Z.
K denotes a set of parameters that must be evaluated (Mwabu, 2009).
Through regression analysis, equation (11) is used to approximate the IV as the Two
Stage Least Square (12). The researcher regress X on K in the first step to get anticipated X
values
We regress Y on in the second stage, with the coefficient on being the Two Stage Least
Square estimator:
Y= α+ β + + …13
Significance (299)
The Importance of the Research is that being aware of the link between health and
poverty outcomes will aid in the development and implementation of effective interventions that
are tailored to the needs of the poor. The findings of the study have the capacity to help
policymakers on economic health designs and the implementers in developing intervention
programs that are bi-dimensional in their approach to addressing both poverty and ill health
outcomes. It will also serve as a reference point for action by nongovernmental organizations,

14
civil society organizations, and other health sector actors that wish to advocate for the
establishment of pro-poor health-care policies in their respective countries. Health and poverty
outcomes have been viewed as separate issues in the policy initiatives that have been
implemented. Because of this, the study serves as a signal to policymakers on the necessity for a
shift in strategy. To conclude, the study adds to the body of empirical research on poverty and
infant mortality that has already been conducted using data from censuses and health surveys,
and it provides a foundation for future research.
There is a pressing need for a societal commitment to spend more and effectively in
people on a more sustained basis. All of the Sustainable Development Goals (SDGs) related to
education are jeopardized if children are unable to read. Putting an end to severe financial
poverty, malnutrition, and malnutrition is just as crucial as putting an end to learning poverty. To
attain it in the conceivable future, we will need to make significantly more rapid development at
a far larger scale than what we have seen thus far. Lastly, the research of poverty helps us
understand a country's economic and social progress. By analyzing poverty, we can devise
strategies to reduce its effect on health and child mortality.

15
References
Adams et al., (2003) “Healthy, Wealthy and Wise? Tests for Direct CausalPaths between Health
and Socioeconomic Status”, Journal of Econometrics, 112: 3-56
Ahmed et al., (2012). On the casual link between poverty and HIV in Nigeria 19902009:
Application of Granger causality and co-integration techniques. Malaysia Journal of
Society and Space. 8 (1): 50 - 59
Ajakaiye, O and Mwabu, G. (2009). The Causal Effect of Socioeconomic Status and Supply-
Side Factors on Health and Demand for Health Services: A Survey of
Elmahdi, H. (2018), “Socioeconomic determinants of infant mortality in Africa: Analysis of
Africa DHS 2003”. Journal of humanities and social science, 2(2):4-14
Foloko, N. (2009) Determinants of child mortality in Lesotho. Unpublished Masters of Arts
Research Paper. University of Nairobi
Frijters et al., (2005) “The Effect of Income on Health: Evidence from a Large Scale Natural
Experiment”, Journal of Health Economics, 24: 997-1017
Fuchs, V.R. (2004) “Reflections on the Socio-economic Correlates of Health”, Journal of Health
Economics, 23: 653-661
Goudge, J. and Govender, V. (2000) “A Review of Experience Concerning Household Ability to
Cope with the Resource Demands of Ill Health and Health Care
Grant, U, (2005) Health and Poverty Linkages: Perspectives of the Chronically Poor. Available
at www.chronicpoverty.org.

16
Gravelle, H, John W, and Matthew, S. (2000) Income, Income Inequality and Health: What Can
We Learn from Aggregate Data? The University of York, Discussion Papers in
Economics, No. 2000/26.
Gwatkin et al., (2000) “Socio-economic Differences in Health, Nutrition, and Population in
Bangladesh”, Washington, DC, World Bank.
http://ideas.repec.org/c/boc/bocode/s425401.html.
Gwatkin et al., (2000) “Socio-economic Differences in Health, Nutrition, and Population in
Bangladesh”, Washington, DC, World Bank.
http://ideas.repec.org/c/boc/bocode/s425401.html. Accessed on 21st May 2013
Gyimah, S. O (2002) “Ethnicity and infant mortality in Sub-Saharan Africa: The case of Ghana.”
Population Studies Centre, University of Western Ontario, Canada.
http://www.ssc.uwo.ca/sociology/popstudies/dp/dp02-10.pdf. Accessed on 15th April
2014.
Judge, K, et al. (1998), “Income Inequality and Population Health”, Social Science and
Medicine, 46 (4-5): 567-579.
Kiringai, J and Manda, D. (2002). The PRSP Process in Africa. A paper presented at the Second
Meeting of the African Learning Group on the Poverty Reduction Strategy Papers on 18-
21 November 2002 in Brussels, Belgium
Klaaw, van der B. and Wang, L. (2003) ‘Child mortality in Rural India, World Bank Working
Paper, Washington DC: World Bank.

17
Larson K and Halfon N. (2010). “Family income gradients in the health and health care access of
US children”, Maternal Child Health J. 2010. 14 (3): 332-342.
Lwanga-Ntale, C. and McClean, K. (2004) “The face of Chronic Poverty in Uganda from the
Poor’s Perspective”, Journal of Human Development. 5 ( 2): 177-194
Mariara et al., (2012) “Child Survival, Poverty and Inequality in Africa: Does Physical
Environment Matter?”, African Journal of Social Sciences. 2 (1): 65-84.
Mariara et al., (2012) “Child Survival, Poverty and Inequality in Africa: Does Physical
Environment Matter?”, African Journal of Social Sciences. 2 (1): 65-84.
Mutunga, C. (2004), Environmental determinants of child Mortality in Africa.
Mutunga, C. (2004), Environmental determinants of child Mortality in Africa. Unpublished
Master of Arts Research Paper. University of Nairobi.
Mwabu ,G (2008) “The Production of Child Health in Africa: A Structural Model of
Birthweight”. Journal of African Economies; 18 (2): 212-260
Ngigi, S (2013), Determinants of Infant Mortality in Africa. A household Level Analysis.
Unpublished
Odongo, C. and J. Karanu (2004) ‘A case study on the level of involvement of the health civil
society organisations in the elaboration and implementation of Africa’s PRSP/ERS.’
Consumer Information Network.
Paxton C & Schady, N (2004). Child Health and the 1988-1992 Economic Crisis in Peru, Policy
Research Working Paper No.3260. The World Bank, Washington D.C.

18
Pryer, J, Rogers, S. and Rahman, A (2003). Work disabling illness and coping strategies in
Dhaka slums, Bangladesh, CPRC conference paper.
Rosenzweig, M. and Schultz, P. (1983) “Estimating a household production function:
heterogeneity, the demand for health inputs and their effects on birth weight” Journal of
Political Economy, 91 (5): 722-746
Smith, J. (1999) “Healthy Bodies and Thick Wallets: the Dual Relation between Health and
Economic Status”, Journal of Economic Perspectives, 13:146-166.
Utilization”, EquiNet Policy Series no. 3. EQUINET, Centre for Health Policy, Wits University
and Health Economics Unit, University of Cape Town
Wichman, J. (2016) “Potential Influences of Cooking and Heating fuel on 1-59 months mortality
in South Africa” University of Pretoria Chapter edition.
Wolfson et al, (2010) “Relation between income inequality and mortality in Canada and in the
United States: cross sectional assessment using census data and vital statistics”. British
Medical Journal, 320: 898-902.
Wright, J. H. and Yogo, M. (2012) “A survey of Weak Instruments and Weak Identification of
Generalised Methods of Movement”. Journal of Business and Economic Statistics, 20
(4): 518-529
Younger S, (2011) Cross-Country Determinants of Declines in Infant Mortality: A Growth
Regression Approach. CFNPP Working paper no. 130.
19
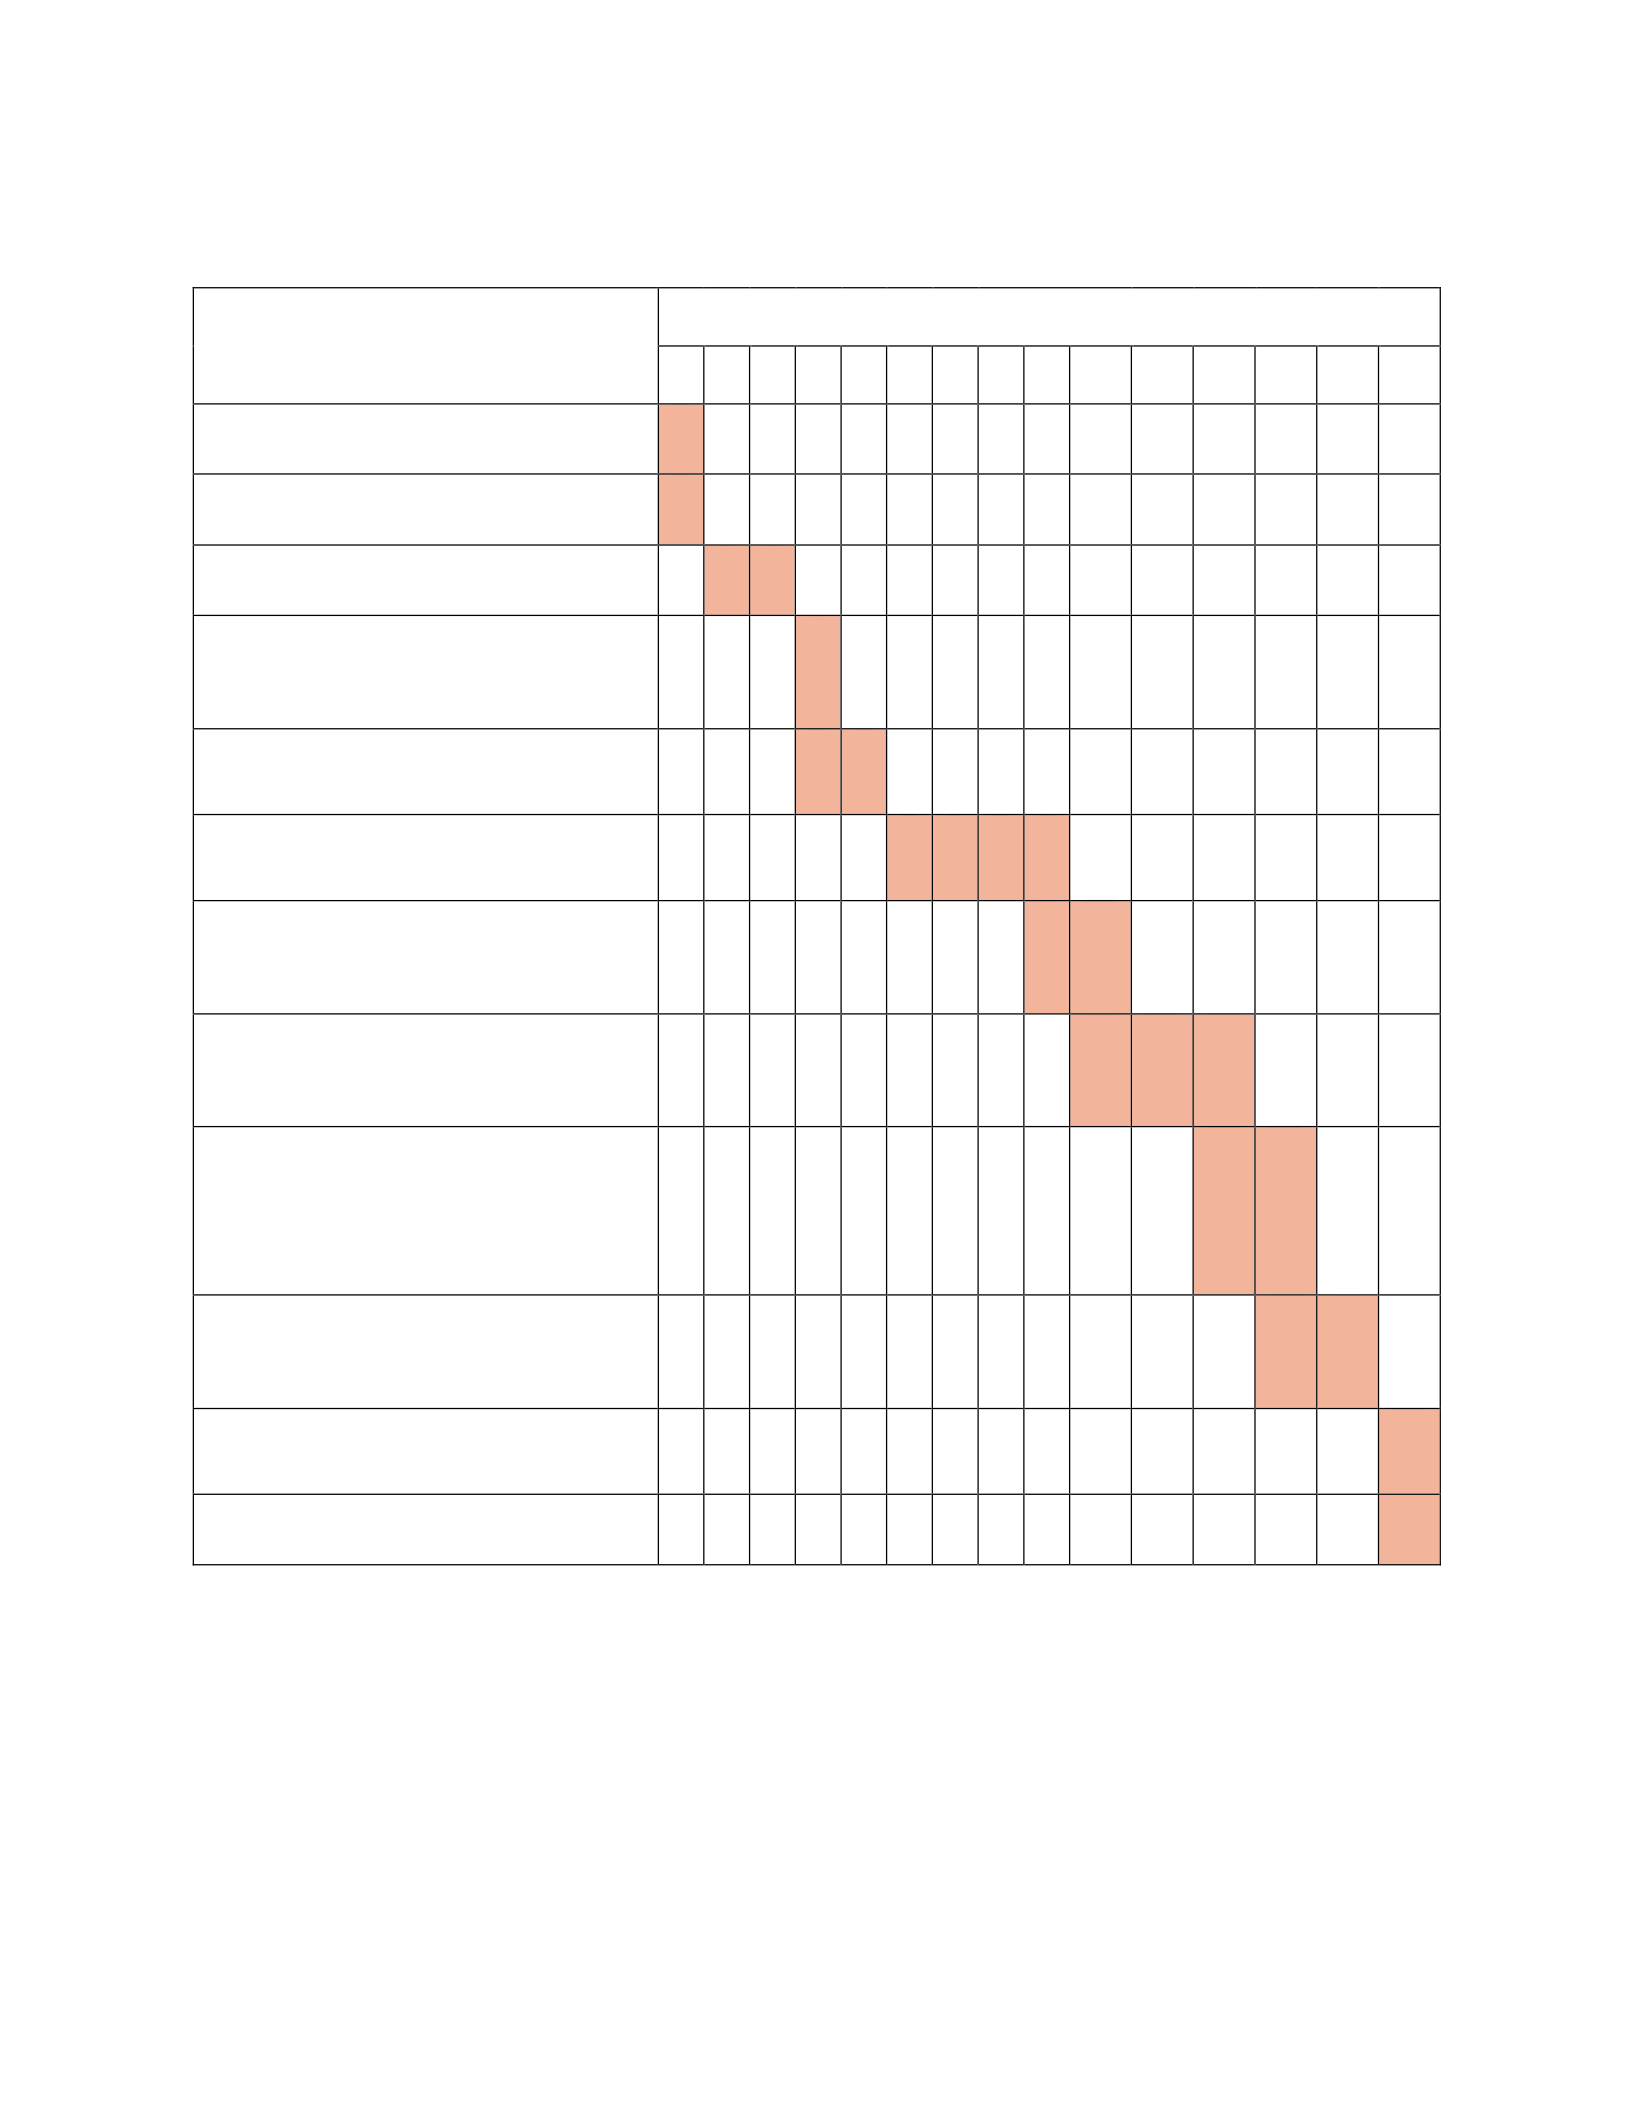
Appendix
ACTIVITY
WEEK
1
2
3
4
5
6
7
8
9
10
11
12
13
14
15
Find a supervisor
Finalize research proposal
Detailed literature review
Finalize Aims, Objectives and
Research Questions
Finalize Analysis for Equation 1,
2, 3&4
Finalize Analysis for Equation
5&6
Finalize Analysis for Equation
7&8
Finalize Analysis for Equation 9,
10, 11, 12 &13
Draft research report after
incorporating supervisor's
feedback
Final consultation with
supervisor and draft revision
Proofreading, printing and
binding
Submit the report

