


Limited Health Access and Education for Vulnerable Families
Families living in poverty with stresses such as job instablility, food insecurity, housing turbulence,
single parent homes, racial prejudice and poor health are vulnerable and less likely to have access
to health care or to receive health education (1-5). Access to regular health care is diminished for
those in poverty, people of color, and those without insurance (6, 7). Newacheck, Hughes and
Stoddard revealed in 1996 the great disparity in primary care for poor, racial minority, and
uninsured children. Reviewing a national data set, they found that minority children and children
in poverty had significantly less access to a usual source of care and were nearly three times more
likely to have inconsistent pediatric provider relationships (1). Additionally, this study found that
children from poor families had 44% fewer medical appointments and were about 50% more likely
to go without treatment for common, yet significant health problems (1). This research team later
found that poor and “near poor” children were three times as likely as non-poor children to have
unmet health needs (2). While health insurance for children can bring families into more regular
care (3, 6, 7), one recent study found that low-income children, regardless of insurance status,
attended only 41% of the recommended preventive health visits (7).
While families receive health information from many sources in their community, limited access
to a pediatric primary care provider means that low-income, minority, and uninsured or
underinsured families are not receiving necessary health messages and education. In their
appointments with health care providers, parents expect to learn about parenting and child
development in addition to physical health care (8, 9). With reduced preventive, well child visits
and less health care provider counseling, however, this expectation is not being met (7, 9) and
families are left without vital health and parenting education. Examining physician advice on

preventive care topics, low-income families receive preventive advice less than half of the time
(7). Even when families are able to attend well child visits, pediatric providers are stretched thin
with shortened visit times and reduced reimbursement rates for well child care and are frequently
unable to incorporate enough health education into well child visits (8, 10).
Stressful home environments further impede the access and education of families in poverty. Stress
adversely effects children’s physical, emotional, and behavioral development (4) and also
diminishes a family’s ability to access health care (5). In a study evaluating the relationship
between family stress and access to care, family stress was found to be “significantly and inversely
associated with confidence about receiving medical care” and “having health care needs met” (5)
. Further, among all children on public health
insurance who presumably have better access
to health care, children in stressful family
environments were less likely to have received
well child visits (5).
Bronfenbrenner’s Social Ecological
Framework
The challenge in addressing the health needs of
vulnerable families is that their health is not
confined within the child or the family.
Instead, each individual is affected by their
surrounding community and neighborhood and more broadly by social, economic, environmental
and political conditions that impact and change their health. Urie Bronfenbrenner applied a “social
ecological framework” to a child’s development, recognizing the multiple “layers” of influences
Figure 1. Bronfenbrenner’s Social
Ecological
Framework.
Source: Adapted from Shumaker, Ockene, and Riekert 2009.
Macrosystem
+
Exosystem+
Mesosystem
+
Microsystem
+
Child+
School&
Family&
Workplace&
policies&
Educa5onal&&
legisla5on&
Cultural&
values&
Societal&&
Norms&
Laws&

in a child’s life from “microsystem” to “macrosystem” (see Figure 1) (11, 12). In the social
ecological framework, a child lives within his or her microsystem, where they have direct contact
with family, child care providers, health care providers, and their neighborhood. The connections
between the structures within the microsystem also have the potential to influence a child’s
development, creating the mesosystem. The exosystem does not directly interact with the child,
but influences the entities in the microsystem, by limiting job hours or changing school legislation.
The macrosystem then includes laws, societal norms and cultural values, which influence the
exosystem (11, 12). This model provides insight into the varied people and structures that influence
a child’s ability to be healthy. Work at any of these levels can change the health of a child and it is
important to be able to recognize the multitude of factors in a child’s life. As health care providers
and health systems are only part of this model, it is important to think of innovative ways to support
families more comprehensively within their individual social ecological framework.
The Medical Home: A means to improve care
The term “medical home” was first defined in 1967 by the American Academy of Pediatrics (AAP)
as “a single source of all medical information about a patient” (13). This definition has broadened,
acknowledging the needs of patients, their role as partners in their health care, and the layers of
other factors that influence a family’s health. The AAP now defines a medical home as a model of
care that is “accessible, continuous, comprehensive, family centered, coordinated, compassionate
and culturally effective” (14) and delivered by a provider known to the family in a relationship of
mutual responsibility and trust. Clinics and providers that function as medical homes recognize
that the family is the “constant” in a child’s life and that they must partner with them to ensure the
best possible health of the child (14). Further, the provision of appropriate referrals to community
services and appropriate care coordination between these caregivers is a critical part of this model

(14), offering patients the wrap-around services that they need to access and carry through their
care plans. Indeed, the Affordable Care Act, national policy makers, child health professionals,
insurers, and quality assurance panels endorse this model as a means of providing a high level of
comprehensive medical care in a cost-effective manner (1518).
Benefits of a Medical Home
Several studies have sought to quantify the impact of medical homes on children with and without
special health care needs (19-24). For children with special health care needs, the medical home
model has enabled more cost effective and comprehensive care. A review of studies on the
effectiveness of the medical home model revealed that for children with special health care needs,
outcomes such as family centeredness, effectiveness, timeliness, health status, and family
functioning were better for children in medical homes than those in standard care (19). Another
study showed that pediatrics clinics that assumed more of the attributes of a medical home were
less likely to hospitalize children with special health care needs and that these children had fewer
emergency room visits (20). Looking at a cohort of all children with and without special health
care needs nationally, children without a medical home are almost four times more likely to have
unmet health care needs (21) and are significantly more likely to have gone without a visit in the
past year (21). Children with a medical home have increased odds of going to preventive care visits
and are less likely to have outpatient or ED sick visits (22). They also have improved parental
assessment of child’s health and are more likely to report health-promoting behavior (including
daily reading, sufficient sleep, helmet usage, and limited daily screen time) (22).
Medical homes have the potential not only to provide improved health care for children, but also
to provide families with necessary health education. The qualities that comprise a medical home,

including familiarity and trust with one provider, also improve patient’s access to health education
and motivation to change behaviors (25-27). Patients who trust their providers are more likely to
adhere to clinician counseling (25, 26). Nelson et al found that patients who rated their health care
provider highly for the attributes of a medical home, including trust, compassion and family-
centeredness, were more likely to receive anticipatory guidance (27). Interestingly, trust, more so
than compassion or family-centeredness, was most strongly correlated with behavior change (27).
Inequity in Access to Medical Homes
The benefits of a medical home are limited, however, to those that have access to them. A recent
study evaluating the 2007 National Survey of Children’s Health found that 56.9% of children ages
1 to 17 had a medical home (21). This study by Strickland et al also found that nonHispanic white
children were most likely to have a medical home (67.3%) and Hispanic and African American
children are less likely, 37.9% and 43.9%, respectively (21). Only 28.6% of non-English speakers
had a medical home. Similarly, a lack of a medical home was associated with low household
income, low maternal education level, and sub-optimal perception of the child’s health (21). These
data further suggests that efforts need to be more targeted at vulnerable, low-income families and
ethnically and racially diverse neighborhoods. Some studies encouragingly report that the medical
home could help close this racial and socioeconomic gap
(28), yet further efforts need to be made to reach other vulnerable populations.

Graber
10
Further Extending the Medical Home
In order to meet the health needs of these families, innovative approaches must be sought. Much
has been written about the need for pediatric healthcare providers to partner with lay health
advisors or child and family advocates, such as child care providers, to provide necessary support,
supplement health education, and facilitate a connection to a medical home (8, 29-32). Globally
and domestically, lay health advisors or community health workers are increasingly being used to
connect isolated populations to health care (33, 34). We hypothesize that family child care
providers are currently acting in this capacity as they are members of the community that they
serve and are connecting families to needed health services and education.
Community Health Workers
The American Public Health Association defines a Community Health Worker (CHW) as “a
frontline public health worker who is a trusted member of and/or has an unusually close
understanding of the community served” (35) . This “trusting relationship” in turn allows them to
connect the community to health services in a more effective and culturally appropriate manner.
CHWs can assume any number of roles: “While in some cases CHWs perform a wide range of
different tasks that can be preventive, curative and/or developmental, in other cases CHWs are
appointed for very specific interventions” (33). The diversity of responsibility and communities
makes it a challenge to assess the role of CHW in health care delivery and health messaging and
numerous studies reveal conflicting evidence as to the effectiveness of community health workers.
Nonetheless, several reviews and studies have found that they can improve health outcomes (33,
34, 36, 37), community health knowledge (34, 38), behavior change (34, 38), and particularly
access to care (34, 37). One randomized controlled study looked specifically at the role of
“community mothers,” meaning mothers identified from within the same community as the
research participants, in providing education about parenting and child development (39).

Graber
11
This study found that the children of first time mothers who were regularly visited by a community
mother were more likely to have their primary series of immunizations, to be read to, and to have
a better diet (39). The new mothers in this study were also less likely to express concerns of
depression and isolation (39).
Other studies of community health workers, however, have been unable to show statistical
significance in the comparing health interventions with community health workers to those without
(33, 34, 36, 40, 41). For example, a randomized controlled study evaluating a community health
worker intervention to reduce diabetes risk factors revealed modest nonsignificant declines in
HbA1c, diastolic blood pressure and triglycerides (40). Interestingly, however, when these
community health workers collaborated with a public health nurse, these improvements became
statistically significant, implying a benefit in collaboration of community health workers with
existing health care systems (40). While the effectiveness of community health workers continues
to be explored, initiatives promoting training and professional and institutional support appear
more beneficial (33, 42, 43).
Role of Child Care Providers
Over fifteen million children under the age of five years old, 65.1% of this age group in the U.S.,
are enrolled in nonparental child care (44). In Connecticut, 70.5% of children under age five are
in nonparental child care, also known as day care, including licensed center-based care, licensed
home-based family child care, and care with a relative, babysitter or nanny (44). Child care centers
in Connecticut take care of more than 12 children per classroom, whereas home-based family child
care (hereby referred to as family child care) care for less than 6 children within the child care
provider’s private home (45). Research has shown that high-quality child care programs are
associated with increased school readiness (46), improved academic higher rates of adult
employment (47), and increased adult earnings (48).

Graber
12
Despite the benefits of high-quality child care, economically disadvantaged children are more
likely to be cared for in family child care settings and are disproportionally enrolled in mediocre
quality child care programs (49). Children in family child care programs are vulnerable as often
these care givers have fewer resources and less training to meet the needs of children already in
need of additional support (50). Further, low income communities have highly variable quality of
child care, making it more challenging to study the effects of child care on early childhood learning
and development (51). Additionally, one study found that low-income children in homebased child
care settings may have greater behavior problems than low-income children in center-based care,
which is attributed to constrained choices for child care providers by parents who are “under strong
and immediate pressure to work outside the home” (51).
Role of child care providers in health promotion
As low income and vulnerable families often depend on nonparental child care and regularly
interact with their child care providers, the child care setting is a natural site for health education
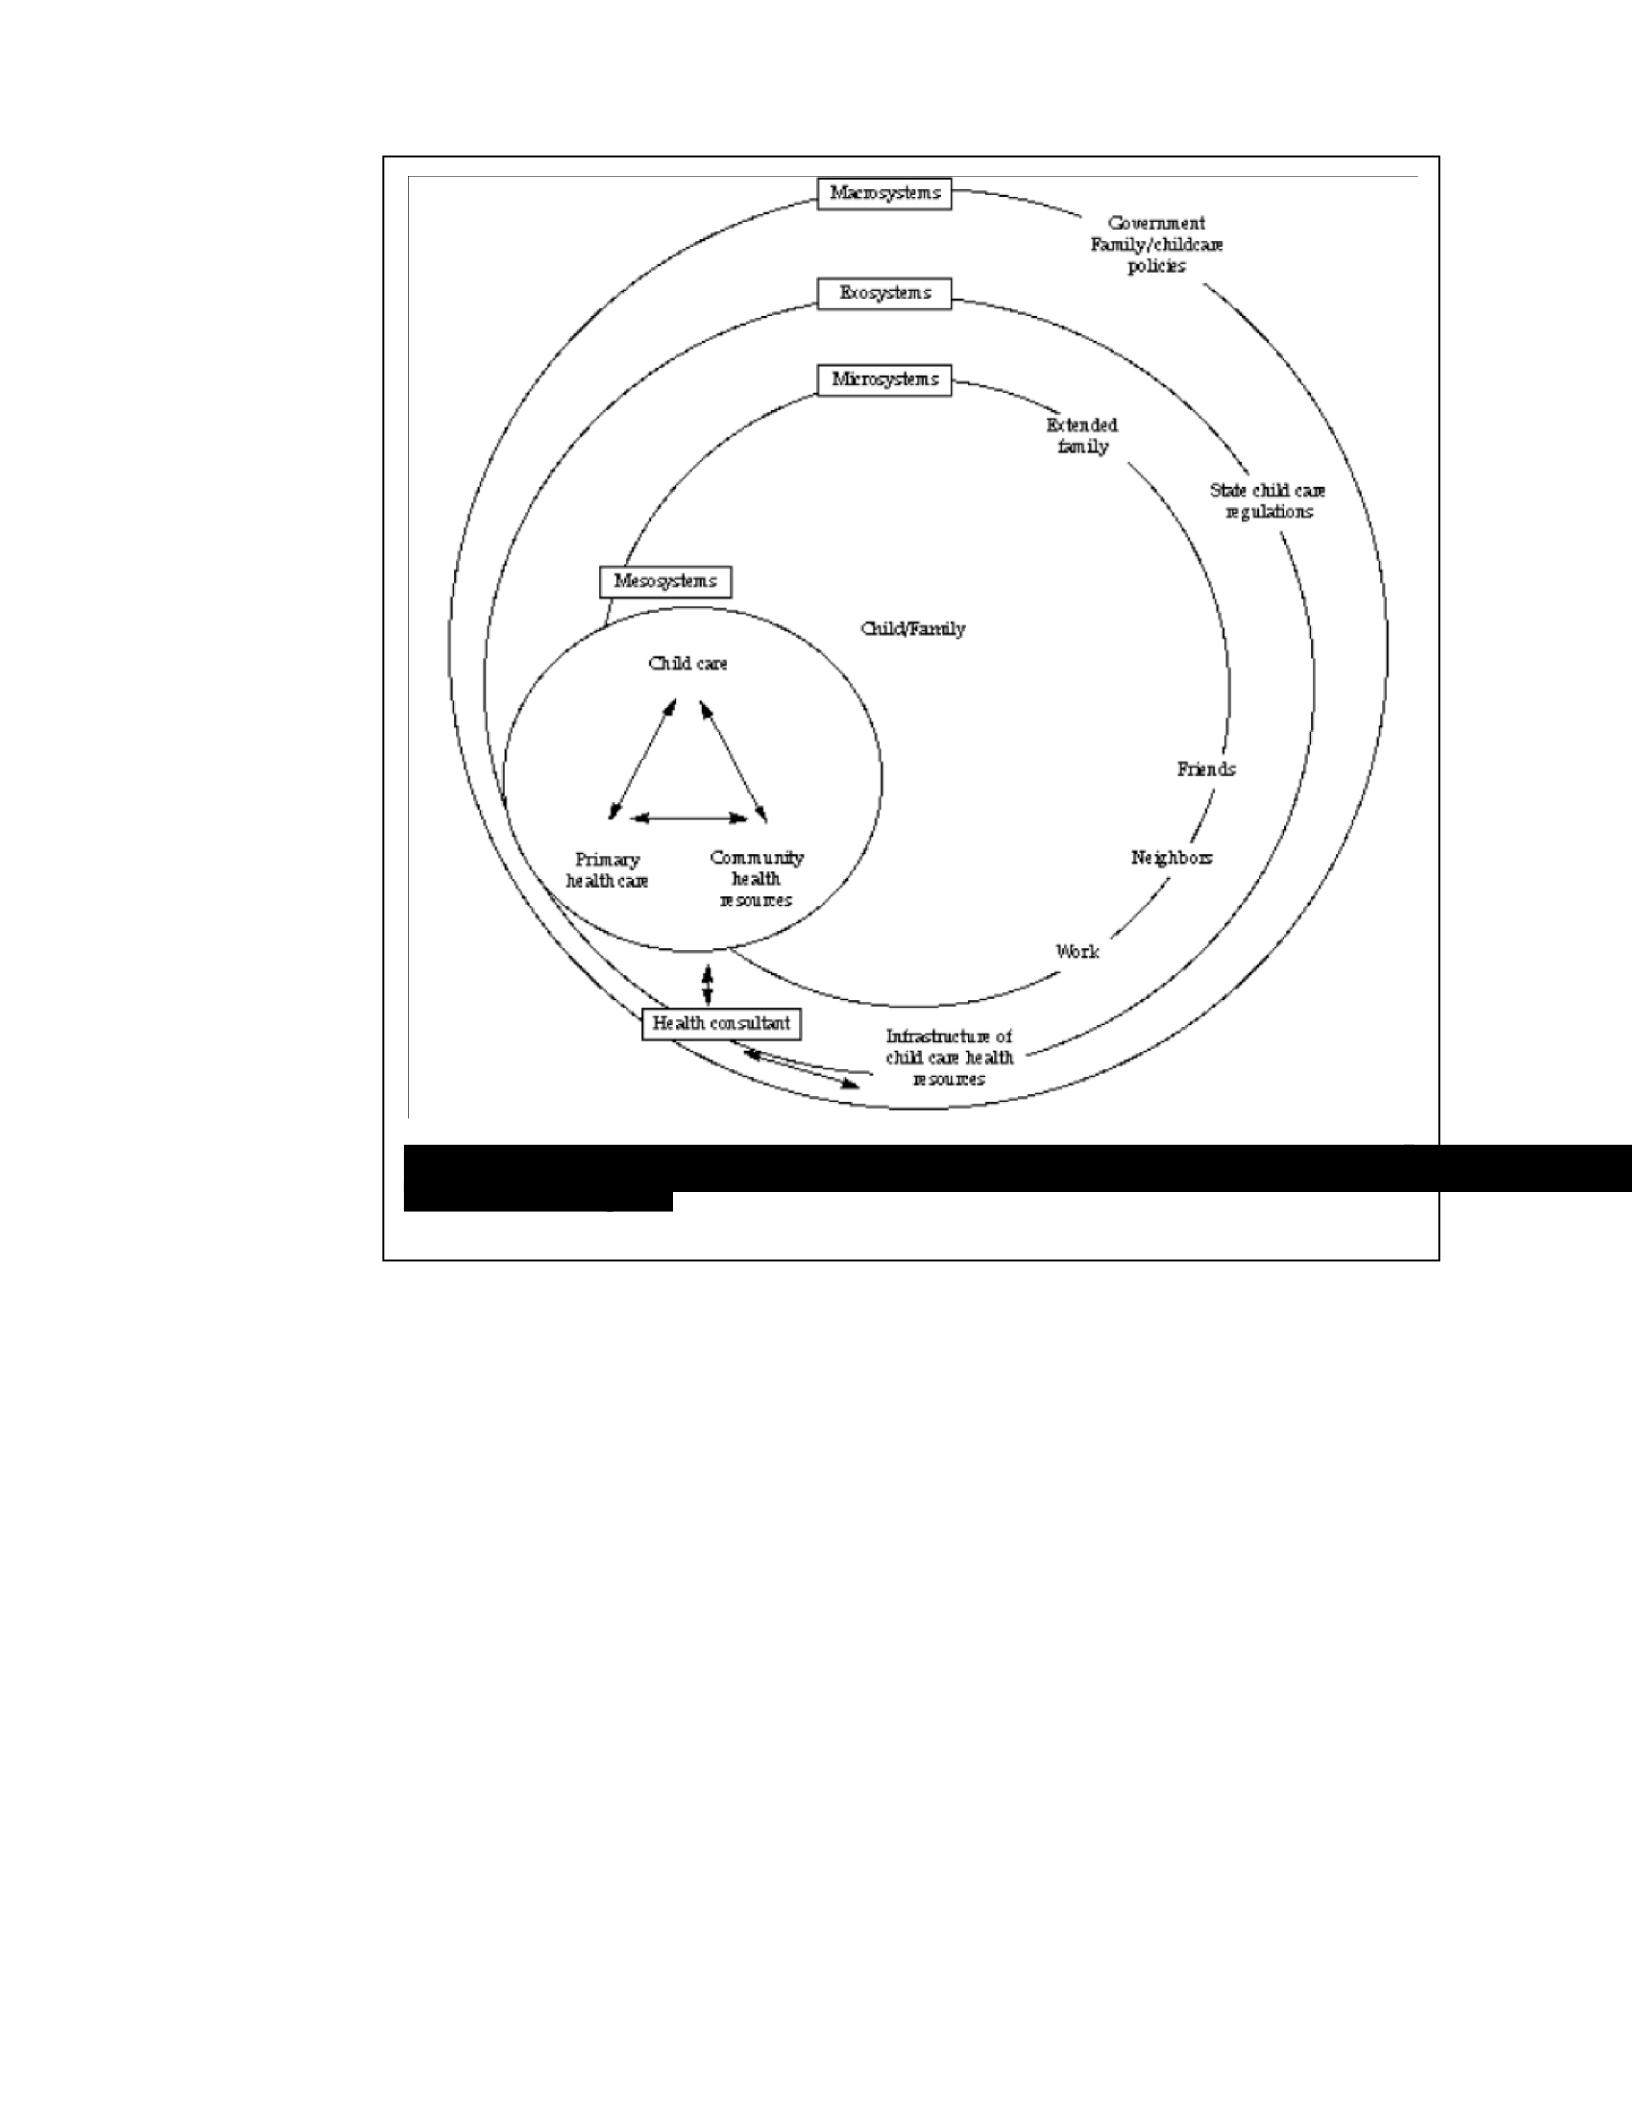
and promotion (31). Angela Crowley has examined the relationships between families, child care
providers and health care providers, particularly in defining the role of the health consultant, a
health professional who serves as a consultant to a child care center (52, 53). In addition to
identifying barriers and strategies to improve collaborative health consultation (52), Crowley has
also contextualized these various individuals within Bronfenbrenner’s social ecological framework
(see Figure 2) (53) . She identifies the individuals who work in the mesosystem (health consultants)
as critical in linking those in the microsystems, which include families, child care providers, and
health care providers. The larger exosystem then includes child care
Graber
13
regulations, child care program inspections and child care health resources. This model, Crowley
argues, acknowledges the myriad of influences on a child’s health while they are in child care (53).
Within this context, the potential for child care providers to promote healthy messages and connect
families to care is considerable.
The training of child care providers to become community health workers, advocates or liaisons
has potential to improve health outcomes of families and children in need. Previous
conditionspecific efforts or specific interventions where health care providers facilitated the
development of this role have proven beneficial for children and families (54-59). For example,
Moon and Oden created a training program for child care providers educating them about the risks
Figure 2. Crowley’s Ecological Model of Child Care Health Consultation.
Source: Crowley, 2001.

Graber
14
of SIDS and the importance of placing infants in a supine position to sleep. Following the
interventional training, the percentage of child care providers who placed children in the supine
position six months later increased from 45% to 78% (54). In another study, Gilliam provided
mental health consultation to child care providers and found that providers reported decreased
oppositional behaviors and hyperactivity in the children under their care (55).
Only a few studies have explored directly the role of child care providers as health educators and
advocates (31, 32). A cross-sectional study by Gupta et al in 2005 distributed surveys to directors
of child care centers, health consultants, and parents inquiring about the barriers to, attitudes
towards, and strategies for integrating health promotion in child care settings (32). They found that
approximately 45% of parents reported receiving health information from their child care center.
Parents (89%), child care directors (88%), and health consultants (80%) thought that health
education in child care centers would be beneficial for families (32). Parents surveyed expressed
interest in learning more about (in descending order of interest) behavior/discipline, managing
emergency situations, developmental issues, nutrition, safety/accident prevention, and
hearing/vision/language problems (32). Barriers to providing health education were lack of
funding, lack of someone to provide the information, and lack of time (32).
Another study by Taveras et al in 2006 collected qualitative data from focus groups with parents
and center-based and family child care providers to evaluate successful strategies for and barriers
to health promotion in the child care setting (31). The focus groups reflected that family child care
providers had less access to health promotion resources than center-based providers, unless they
were affiliated with umbrella organizations that provided professional development and trainings.
Parents expressed confidence in family child care providers because “they see kids all the time”
(31) and family child care providers expressed comfort sharing advice based on their own

Graber
15
experience as parents. Child care providers wanted to communicate better with the children’s
pediatricians (31).
For the last several years, Dr. Marjorie Rosenthal has collaborated with the New Haven nonprofit,
All Our Kin, whose mission is to educate and empower parents and teachers, give families child
care choices, and expand access to high-quality early care and education (60) . Together Rosenthal
and All Our Kin have explored the complex relationships between child care providers and families
in addressing the health needs of children, building on the previous literature. In a qualitative study
evaluating family child care providers experiences in health promotion (29),
Rosenthal interviewed 17 child care providers and identified recurring themes including: 1) Family
child care providers expressed a great sense of responsibility for each child’s health, wanting to
promote healthy eating, lifestyle, and development for each child in their care; 2) Child care
providers acknowledged that they provide support and education for families on issues of
discipline, skin care, and nutrition; and 3) The depth of relationship between the child care provider
and the family changes the health education that the child care provider shares (29). While
Rosenthal found that child care providers identify a definitive role for themselves in health
promotion, she also noted that the providers were sensitive to parents’ concerns that their
promoting health could be “stepping over the line.” “Child care providers are able to extend their
role beyond traditional topics of health promotion only when they have a collaborative relationship
with parents; they are restricted when the relationship is conflicted” (29) . Child care providers
expressed that they circumvent these conflicted relationships with parents by using humor,
avoiding jealousy, establishing a comfort zone, and gaining trust (29).
In another paper, Rosenthal further explored the perspectives of family child care providers
specifically on child development and behavioral health (30). From this study, the following

Graber
16
themes emerged: 1) Providers shared that they often observe and assess children, altering their
programming for the various developmental levels and the needs of the children under their care;
2) Child care providers advise parents about strategies and resources for development and
behavior, discuss medications, and advocate for extra support in school for the children who
concern them, and 3) Child care providers acknowledged their limitations in facilitating improved
health, development, and behavior (30). They identified barriers such as their own educational
background, their difficulty handling challenging children and resistant parents, and recommended
means to further develop these skills (30).
STATEMENT OF PURPOSE
One innovative idea is to consider the role that family child care providers, especially those serving
children living in poverty, could play in decreasing the inequity in access to a medical home. While
prior research has revealed that family child care providers identify themselves as health educators
and advocates, there are limited data on how parents, health care providers, and community service
providers perceive child care providers in these roles. Prior to embarking on an intervention that
might create partnerships across these professional and personal domains, it is important to know
how these three groups of people perceive the potential role of child care providers as current or
potential advocates, community health workers, or care coordinators. Accordingly, this thesis seeks
to characterize how parents, health care providers, and community service providers experience
and perceive this role in order to assess and develop future trainings and support services
promoting children’s health.

Graber
17
SPECIFIC AIMS
In effort to evaluate the potential role of child care providers as health educators and advocates for
medically underserved families, we interviewed 1) parents, whose children are cared for in home-
based, family child care, 2) health care providers, and 3) community service providers about their
perceptions of this role. Our specific aim was:
• To gain a greater understanding of the perceptions of underserved parents, health care
providers and community service providers regarding the role of family child care providers
as resources for health education and advocacy.
We hypothesized that parents receive health information from a myriad of sources but that their
relationship to their children’s family child care providers elevates the importance, relevance, and
desire to adhere to the health information parents receive from child care providers. Further we
anticipated that health care providers and community service providers do not currently utilize
child care providers to disseminate health information nor to serve as a conduit for health care
access, but that they perceive a collaboration between the two may be feasible.

Graber
18
METHODS
Study design and sample
We conducted a qualitative study using in-depth, in-person interviews of parents, health care
providers, and community service providers whose children and patients utilize family child care
providers. Community service providers were defined as those who work for agencies that serve
young children and families in greater New Haven, such as home visitors, community organizers,
early intervention providers, and care coordinators. A qualitative method is suitable for studying
complex social interactions and enables characterization of the subtle processes of role negotiation
sought in this study (61-63) .
Further, this study used a community-based participatory research (CBPR) approach. CBPR is an
approach to research that is participatory, values co-learning, and cooperation that engages
community members and researchers to work collaboratively and contribute equally while
promoting systems development and local capacity building (64) . There are three ways that this
project used a CBPR approach, as defined by the Agency for Healthcare Research and Quality
(AHRQ) (65, 66) . First, this project was informed by “participation by representatives of
organizations and research in all aspects of the research process” (66) . The study was initiated in
partnership among an academic researcher (MSR) and the executive director of All Our Kin (JS),
a local agency promoting professional development and education of family child care providers.
The academic researcher and this student researcher (LKG) chose to collaborate on the project.
The project ideas were then presented to the New Haven Early Childhood Council, comprised of
individuals vested in early child education and health, who provided direct feedback. One member,
the director of Nurturing Families Network in Fair Haven (EF), was recruited to participate in the
project. Further, a community research assistant was hired who, herself, utilized family child care
when her children were pre-school aged, lives in a resource-poor neighborhood in New Haven,

Graber
19
and has children with special health care needs (KJ). These five individuals comprised the
Advisory Group, which helped inform this project, including the recruitment process, interview
tools and incentives, data analysis, and presentation of themes. A smaller core of this group formed
the Research Team, including this student researcher (LKG), the community research assistant
(KJ), and the academic researcher (MSR), which met regularly to review and code each of the
interviews and to identify the main themes and ideas. Second, the study involved “sharing of
decision-making power and mutual ownership of the processes and products of the research
enterprise” (66) . Each member of the Research Team brought unique reflection and analysis to
the interview coding process. The themes were then brought to the larger Advisory Group for
reflection and insight. The interview questions and coding structure were altered to reflect the
questions of the Advisory Group. The Research Team then completed the coding of the interviews
and identification of prominent themes. Third, the “reciprocal transfer of expertise” (66) occurred
through the number of Advisory Group and Research Team meetings including honest
conversations about the analysis and interpretation.
We conducted three simultaneous recruitment processes in greater New Haven. In the first
recruitment process, I identified family child care providers through various child care networks,
such as All Our Kin. I collaborated with individual family child care providers to offer their parents
a health education workshop at their family child care home. I developed and led several health
education sessions on topics of interest to parents, including: flu & colds, healthy snacks &
nutrition, and child development. I invited the parents who participated in the health education
sessions to participate in the study. Additionally, I identified parents through a variety of contacts
with whom we currently have solid, working relationships, including the Nurturing Families
Network and All Our Kin. We attempted to use the “snowball method” of recruitment to expand
our recruitment numbers but were unsuccessful (67) .

Graber
20
In the second aspect of recruitment, I recruited health care providers at the principal locations in
New Haven providing primary care to underserved children: including Hill Health Center, Fair
Haven Community Health Center, Yale Primary Care Center, and St. Raphael’s Hospital Pediatrics
Clinic. I contacted individuals directly who expressed interest in vulnerable families and
successfully used the “snowball method” in indentifying other providers in the community
(67).
In the third recruitment process, we identified community service providers who advocate for the
health of young children and their families. The Advisory Group and the New Haven Early
Childhood Council identified these individuals. The “snowball method” of recruitment was
successful in identifying other community service providers (67) .
I conducted interviews until thematic saturation was achieved. Thematic saturation occurs when
no new concepts emerge from reviewing successive data from a sample diverse in experiences and
pertinent characteristics (68) . As sample size varies depending on the breadth and complexity of
the inquiry, it was not possible to predict the number of participants in advance. In this study, we
reached thematic saturation at 11 interviews with parents, 12 interviews with health care providers
and 25 interviews with community service providers.
Data collection and methods
The investigators refined the interview guides using the Advisory Group, experts in pediatrics and
child care, and qualitative methods. The interview guides were piloted using two parents, two
health care providers, and two community service providers and the instruments were refined in
an iterative manner (Tables 1, 2 & 3). I used open-ended questions to carry out each face-to-face,
in-depth interview. The guide for parents of children in family child care utilizes general and

Graber
21
nondirective questions to elicit parents’ perceptions of 1) their children’s access to health care and
2) their family child care provider providing health education and advocacy. The guide for health
care providers and community service providers similarly seeks to extract their perceptions of 1)
access to health care for low-income families in family child care, and 2) the role and ability of
family child care providers to function as health educators and advocates. Following the interview,
each parent was asked demographic questions including age, race, household income, education
level, employment, and number of children in child care. Health care providers and community
service providers were asked similar questions, including years working in the community (Table
4).
Written informed consent was obtained prior to each interview. Parents received a $50 gift
certificate for their participation. The Human Subject Committee at Yale University approved the
study.

Graber
22
Table 1. Interview Guide for Parents
Introductory questions
1. Please tell me about how you chose the family child care program where your child currently attends.
Prompts: What is/are your child care provider's(') name(s)? How would you describe what your child does
and learns at family child care?
2. How would you describe your relationship with your family child care provider? Do you feel like your
family child care provider understands you and your family?
Key questions
1. Tell me about the ways in which your family child care provider helps keep your child/children healthy.
Prompt: Please think about the times your family child care provider talked to you about the health of
your child/children. How about when they tried to teach you something about health? Please give me an
example of this. How did you feel about this experience? How has your family child care provider
discussed healthy eating habits for you and your child/children? How has your family child care provider
discussed physical activity with you and your child/children? How has your family child care provider
discussed your child's development with you and your child/children?
2. Think about times when your child has been sick or dealing with an illness or disease. Can you tell me
about the role your family child care provider played when your child was sick or ill? Prompt: Does your
child have any chronic illnesses like asthma or diabetes?
3. Has your family child care provider ever helped you get medical or social services in the community?
4. How important is the role of your family child care provider in your child’s health and development?
5. Sometimes, state regulations change about what immunizations or shots your children need to have prior
to entering child care or school. Have you been affected by these changes? How did you feel about them?
Has your family child care provider ever been the person who told you about the changes in shots your
child needed? Can you tell me about that?
Prompt: Were there any other changes in health recommendations that your family child care provider
was the first to tell you about?
6. Some child care providers are licensed from the state. Do you think this affects how they take care of your
child?
Other providers have a certificate showing that they have taken classes on child development. Does this
affect how they take care of your child?
7. Where are places or who are the people you turn to for health advice? For example, when you learned
first heard about the flu and flu vaccine, who did you trust to give you information about this? Who do
you trust about health advice in general?
8. What would you do if you thought your child had developmental delay? Prompt: Who would you call?
Who would you ask for advice?
9. Now thinking about programs for children and families in New Haven, can you tell me some of your
favorites? What are things that make these programs great? Prompt: What do they do?
10. What do you think about your health care provider’s (your doctor’s or nurse’s) knowledge of resources
for families (such as social services and early childhood programs) in New Haven? Were they able to give
you the information that you needed?
Prompt: When you go to your health care provider, what types of things do you learn about? Do you ask
questions? Why or why not?
11. Can you think of any ways doctors or nurses or health care educators or teachers could help your family
child care provider to improve the health of your child?

Graber
23
Final Question
1. Is there anything else you would like to share?

Graber
24

Graber 26
Table 2. Interview Guide for Health Care Providers Graber 24
Introductory questions
1.2. Please tell me why you chose to work at [insert name of community health center/hospital]?What do you
consider important about the work you do?
Key questions
1. Think about the young children you have cared for who have chronic conditions, such as asthma, obesity,
or diabetes. Please describe a time when you felt you struggled to educate a family or have them follow a
plan of care.
Prompt: What were some of their barriers in actualizing care? Please give me an example of some
mechanisms that ultimately facilitated their care and/or education.
2. Think about children you have cared for who have developmental, behavioral or mental health issues.
Please describe a time when you felt you struggled to educate a family or have them follow a plan of care.
Prompt: What do you do when you suspect a child has developmental delay? What steps do you recommend
for the family? Who follows up – you or the family?
What were some of their barriers in actualizing care? Please give me an example of some mechanisms that
ultimately facilitated their care and/or education.
*Have you ever been the first one to tell a family that a child has developmental delay?
3. How do you coordinate care for special needs children in your practice? Who is involved on this team? In
an ideal world, how would care coordination function?
4. Please think of the ways you have tried to help a child you cared for get social services and additional
support in the community, like WIC, housing assistance or legal assistance. What have been some of the
more successful ways?
5. What is your sense of what your patients do for child care? Do you think your patients use that?
6. How familiar are you with the different and changing resources available to families in New Haven? How
do you learn about these programs?
7. Have you had the experience where a parent came in saying that the child care provider says that the child
has developmental delay or developed specific behaviors in child care that are concerning? Prompt: Can
you tell me about it? Do you ever talk to the child care provider?
8. Have you ever had a patient whose child care provider gave them health advice? Prompt: Please tell me
more about this experience. How important is it for family child care providers to educate parents about a
child’s health and development?
9. Have you ever collaborated with a child care provider to help promote health or development for a certain
child?
Prompt: One example is an asthma action plan. When you have created medical plans for children, have
you ever consulted a child care provider? Do you think this would be helpful? Can you think of any ways
child care providers could help you with health promotion in the community? Could they help with
ensuring that children have medical homes?
10. Frequently the regulations change about immunizations required prior to entering child care. How do you
learn about these changes? What if you do not agree with these regulatory changes? How do you advise
your patients? How do you feel about family child care providers relaying this information to parents and
families? How do you feel about family child care providers relaying other health information to parents
and families?
11. Who are the people or organizations where your patients are getting health information?
Prompt: Who do they trust to give them health information? When a patient refuses the flu shot, what are
their reasons? Who gave them this information?

Graber 27
12. Could you describe reservations you have about child care providers giving health education in the
community?
Final Question
1. Is there anything else you would like to share?

Graber 28
Table 3. Interview Guide for Community Service Providers
Introductory questions
1. Please tell me why you chose to work at [insert name of community agency]?
2. What do you consider important about the work you do?
Key questions
1. Think about families you have worked with who have had children with chronic conditions, such as
asthma, obesity, or diabetes. Please describe a time when you felt you struggled to help a family with these
concerns.
Prompt: What were some of their barriers to them getting help? Please give me an example of some
mechanisms that ultimately facilitated their getting the help they needed.
2. Think about children you have worked with who have developmental, behavioral or mental health issues.
Please describe a time when you felt you struggled to connect a family to the services they needed.
Prompt: What do you do when you suspect a child has developmental delay? What steps do you
recommend for the family? Who follows up – you or the family? What were some of their barriers in
getting help? Please give me an example of some mechanisms that ultimately facilitated their getting
assistance.
3. Who are the people or what are the organizations where your families are getting health information?
Prompt: Where do people actually get their health information? Who do they trust?
4. Please think of the ways you have tried to help a family get social services and additional support in the
community. What have been some of the more successful ways?
5. What are programs that have been successful at educating families about health? What has made some of
these programs more successful than others?
6. Have you ever had a family whose child care provider gave them health advice? Prompt: Please tell me
more about this experience. Is it important or appropriate for child care providers to educate parents about
a child’s health and development?
7. Have you ever collaborated with a child care provider to reach families?
Prompt: Can you think of any ways child care providers could help you reach communities? Could they
help connect families to services and programs in New Haven?
8. Could you describe reservations you have about child care providers giving health education in the
community?
9. Have you ever collaborated with a health care provider to reach families and connect them to services?
Prompt: Can you think of any ways health care providers could help you reach communities? Could they
help connect families to services and programs in New Haven?
Final Question
1. Is there anything else you would like to share?

Graber 29
Table 4. Demographic Surveys All
Interview Participants
1. How old are you?
2. How do you describe your race/ethnicity (for example, African American, Latino, Caucasian, etc.) 3.
What is your gender (for example, male, female, or other)?
4. What was the highest level of education you received (for example part of high school, completed high
school, some of college, or completed college degree)?
Additional questions for specific interviewees: Parents:
1. How many children do you have or have had in family day care?
2. How many years have you had children in family day care centers?
3. What was your total income last month?
a. Less than $799
b. $800 – $1,249
c. $1,250 – $1,999
d. $2,000 – $2,999
e. $3,000 – $3,999
f. $4,000 – $6,249
g. $6,250 – $7,999
h. $8,000 – $12,499
i. $12,500 – $15,999
j. $16,000 and above
4. Where do you bring your children for check ups and health services when she/he's sick?
5. Do you receive support from Care4Kids? Health Care Providers
1. How many years have you worked in community health clinics?
2. How many years have you been a practicing health care provider? Community Service
Providers
1. How many years have you worked in your current position?
2. How many years have you worked in New Haven?
Data analysis
All interviews were audiotaped and transcribed by a professional transcription service. Verifiable,
systematic analysis was achieved through several strategies, including 1) consistent use of the
interview guides, 2) audiotaping the interviews that were transcribed by an independent service, 3)
standardizing coding and analysis of the data, 4) using researchers with diverse backgrounds for
analysis, 5) creating an analysis audit trail to document analytic decisions, and 6) presentation to
the Advisory Group for confirmation of consistency of findings (69-72) .
First, the interview guides were modified iteratively. While reviewing the transcripts, if we thought
that some areas or discussions needed deeper exploration, we added questions to the interview
guides. This included 1) asking parents about how important they feel their family child care

Graber 30
provider is in helping their child’s health and development, and what they would do if their child
had developmental delay, and 2) asking health care providers what they believe their patients do
for child care and if they have ever had a parent come in with a concern of a child’s developmental
delay identified by the child care provider.
We used the constant comparative method of qualitative analysis to develop and implement
consistent and comprehensive coding of open-ended data. In order to objectively draw themes and
perceptions from the interviews, we developed the coding structure over a series of iterative steps
to conceptualize and classify the information. Specifically, each member of the analysis team
independently read two transcripts, then met to discuss ideas shared in the transcripts, and took
notes on our discussions. This process was repeated three times until we noted recurring ideas in
the transcripts; at that point I developed a preliminary code structure that was then reviewed by the
Research Team. Each member of the Research Team then independently applied the code, line by
line, to an additional 13 transcripts. We met to discuss each person’s coding and to discuss
discrepancies. The academic researcher and I together reviewed and coded an additional 8
transcripts and then met to discuss discrepancies. The remaining 4 transcripts were reviewed and
coded by me independently.
We added to the code as needed and iteratively reviewed the code for logic and breadth. We repeated
this process throughout the project, independently using the constant comparative method until
thematic saturation was achieved and no new themes emerged. Throughout the process, we
reviewed the coding for discrepancies and to negotiate consensus (70) . Using the refined consensus
code structure, I recoded all 31 transcripts independently and the two other investigators reviewed
the coding for consistency.

Graber 31
The interviews and codes were then entered into Atlas.ti 6.2 (Scientific Software Development
GmbH, Berlin, Germany) to facilitate review, analysis, and reporting. For the scope of this thesis,
outputs were sought that related to the themes of family child care providers as community health
workers and the various discrepancies or similarities around health advice. Every quote in each
code was reviewed for key subthemes and individual quotes that summarized these subthemes were
then selected for inclusion in the results. These themes were then presented and reviewed by the
Advisory Group.
RESULTS
A total of 48 individuals were interviewed as part of this study, totaling 32 hours of interviews and
481 pages of transcripts. Of the parents interviewed (n=11), the average age was 34 and the majority
were female (73%) (Table 5). Over sixty percent were African American, 27% were Latino and 9%
were Caucasian. The vast majority of parents had more than a high school diploma, yet nearly half
made under $24,000 per year and all made under $50,000. Remarkably,
Table 5. Characteristics of Parents Interviewed
Characteristics of Parents Interviewed
Characteristic
Age (mean) (n=11)
34 years (Range 22-46)
Race/Ethnicity (n=11)
African American/Black
Latino/Hispanic
Caucasian/White
64%
27%
9%
Female (n=11)
73%
High school diploma (n=9)†
90%
Family Household Income (n=9)*
Less than $50,000/year
Less than $24,000/year
100%
45%
Number of children in family child care (mean)
(n=9)*
1.6 (Range 1-3)
Years in family child care (mean) (n=9)*
2.3 (Range 0.5-6)
Graber 32
Pediatric practice (n=9)*
Academic medical center Private
practice
Community health center
Unknown
44%
44% 0%
11%
Families whose child care is subsidized by the
state (n=9)*
89%
†Data incomplete for two interview participants.
* Two couples were interviewed together, i.e. a mother and father were interviewed at the same time. For demographic questions that referred
to families, answers for families, not individuals, were included.
parents sent their children to either an academic medical center for primary care or private practice.
Families who attended Federally Qualified Health Centers were not represented in this study. Most
parents were interviewed alone, except for two interviews, where both parents were interviewed
together.
The health care providers interviewed (n=12) had a mean age of 50 years with over 17 years of
experience (Table 6). They were predominantly physicians (75%), female (75%) and Caucasian
(75%). Half of the health care providers interviewed worked in a Federally Qualified Health
Center.
Table 6. Characteristics of Health Care Providers Interviewed
Characteristics of Health Care Providers Interviewed (n=12)
Characteristic
Age (mean)
50 (Range 34-70)
Race/Ethnicity
African American/Black
Latino/Hispanic
Caucasian/White
Other
8%
8%
75%
8%
Female
75%
Medical education
Physician
Nurse practitioner
Registered nurse
Masters in Public Health*
75%
17% 8%
17%
Practicing in a Federally Qualified Health
Center
50%
Years in practice as a health care provider
(mean)
17.7 (Range 3-35)

Graber 33
Years in practice in a community health setting
(mean)
15.5 (Range 2-35)
*This degree was in addition to medical training.
Of the 25 community service providers interviewed, demographic data was obtained from only 9
interview participants. The remaining 16 community service providers were interviewed as part of
a focus group where demographic information was not collected. The community service providers
tended to be slightly older, with a mean age of 56 years, and a mean of over 23 years
Table 7. Characteristics of the Community Service Providers Interviewed
Characteristics of Community Service Providers Interviewed†
Characteristic
n=9†
Age (mean)
56 (Range 43-67)
Race/Ethnicity
African American/Black
Latino/Hispanic
Caucasian/White
8%
33%
56%
Female
89%
Education (n=8)*
Some college
College
Graduate degree
13%
25%
63%
Years in current position (mean)
15.8 (Range 2-40)
Years in practice in New Haven (mean)
23.3 (Range 4-47)
† Focus group participants (n=16) were not included in this demographic survey. *
One participant did not provide level of education.
of experience in New Haven (Table 7). All interviewees had some form of graduate education and
were predominantly white (56%) or Latino (33%).
Systematic qualitative analysis revealed six essential themes related to the role of family child care
providers working as community health workers. When characterizing this role and responsibility,
parents, health care providers and community service providers described: I. Families are
struggling to meet basic needs, II. Comprehensive health care is important, but uncompensated, III.
General perspectives on family child care providers giving health education and advice, IV. The

Graber 34
role of communication, V. The role of personal relationships, and VI. Ways for family child care
providers to achieve best practice as health educators and advocates. Further, concerns around
development are particularly challenging for families and child care providers and this case is
articulated further as an example. These themes are characterized below, with quotes from parents,
health care providers, and community service providers to illustrate each.
I. Families struggle to meet basic needs
While parents subtly referred to their own struggles, health care providers and community service
providers expressed concern that families are so occupied with ensuring that their children’s basic
needs are met that they are unable to receive health education. For instance, a community service
provider stated:
I say this because in my experience, lower income families - and not all, not all - are more likely
to wait until - I would say the first indication of something may be going on with their child [i.e.
developmental delay] may come from the school. So ok, when he or she is 2, and not doing
something - you may have other stuff going on. You may not know where your next meal is coming
from. Anything - you may be struggling with rent or you may be in a shelter or whatever your
situation is. And that’s how I think folks take their own healthcare. Health is of course major,
because if you don’t have that, you’re not able to handle all of those things that are coming at you.
But for families who are struggling to meet basic needs, healthcare is so far down the line, it’s so
far down the list. But I think a lot of people will write it off as “He’s acting out,” or “You are just
bad. You’re a bad kid.” (46-year-old community service provider with 15 years of experience in
New Haven)
A community service provider agreed, saying that a child’s health is influenced by their
surroundings and that health care provider recommendations are often out of touch with a family’s
situation:
I don’t think [health is] just located in the people... we know that asthma can be caused by poor
environmental health conditions: roaches or insects, dust, whatever. It also is aggravated by
chronic stress or too much physical activity sometimes and/or stressful activity associated.
Knowing that doesn’t change that for a family. There are a lot of conditions that have to be in
place for the family to actually get out of poverty, to get out of the stressful environments that
they’re living in. They may be living in that house because they left an abusive situation, a partner,
and they’re sleeping at their parents’ house there in the living room, the kid and the parent, and it
may not be their space to actually remove the carpeting... So, there’s an assumption that once you
get diagnosed with this then you need to do x, y, and z… there’s a whole lot of psychological sort
of underlying things that underlie this that actually are not considered, I think, from a medical
perspective. (52-year-old community service provider with 18 years of experience in New Haven)

Graber 35
A health care provider said that when she is able to express understanding of all the possible stresses
facing a family, she is able to reaffirm her personal relationship with them:
I tell them… “I have to know your kid gets enough sleep; I have to know that your kid gets enough
to eat; I have to know that your kid is not depressed; I have to know that one of you is not beating
the other one at home, or that the kid isn’t being abused somewhere.” I tell people that stuff. And
then I say, “And if I know all that, and they don’t have a TV in their room that they’re watching
surreptitiously at night…” So people think… that you really care about their kid. I don’t think this
is difficult. It’s hard in places like episodic care centers where people don’t know each other. (60-
year-old health care provider with 32 years of experience)
II. Comprehensive health care is important, but uncompensated
Health care providers expressed that comprehensive care is important, but rarely compensated.
Several health care providers felt that it was important to connect families with wrap around
services, including schools and child care, but that compensation is a barrier. For example, a health
care provider said:
It’s part of the pediatric practice to engage the school and the parents and sometimes friends and
the therapist in this case, now the diabetes prevention program and the exercise people… There’s
no compensation for any of this—it’s all sort of extra time. But you have to do that if you’re going
to take care of a child well. (45-year-old health care provider with 16 years of experience)
A health care provider said that she needs other people to assist her in care coordination:
[A neighboring clinic is] a formal medical home and they are a big role model where they have
onsite - I think they have a nurse manager and 2 social workers onsite at all times. Someone who
is responsible for that [care coordination] aspect alone. Physicians who have other clinical
responsibilities and don’t have time set aside for that, I don’t think can do it. (35-year-old health
care provider with 6 years of experience)
Further, another health care provider expressed frustration that the issue of compensation constrains
the quality of care she can provide:
We’re always at this tension between do we do an A+ job for every case, and have a very long
waiting list? Or is a B good enough? And it’s a big issue. And we don’t get paid well enough to
do this. So in certain climates we have been told, “Sorry, A+ is nice, but you’re only getting paid
for B. So you better figure out where to cut that.” (50-year-old health care provider with 21 years
of experience)

Graber 36
III. General Perspectives on Family Child Care Providers Giving Health
Advice
Parents, health care providers, and community service providers expressed different perspectives
on family child care providers giving advice to families, centralizing around four main themes.
These themes included that a) family child care providers spend a long time with children and are
accessible to families, b) family child care providers can be an extended part of the family support
system, c) child care providers have experience, but not specific expertise, and d) child care
providers help bring children into regular well child care.
A. Child care providers spend a long time with children and are accessible to
families
Parents and community service providers expressed that because child care providers spend a
substantial amount of time with children, they have a unique role in their lives and may be
legitimized in giving families health advice. The time spent with children, the interviewees reflect,
often enables child care providers with the additional insight into the health, development, behavior
and learning of a child. Health care providers were more measured in their perception of child care
providers’ role in assessing children and giving families health advice.
Parents articulated that in the amount of time they spend with children, child care providers can
have great influence on a child. One father stated:
At that atmosphere where you’re going to be with my child every day for a certain amount of time,
that means it accumulates, especially if you’ve been over there for over three years, that
accumulates to almost a year. It’s like pretty much we had my child for a whole entire year without
me being there. So a person that’s gonna have that much influence on my child, I want to at least
have the best interests for my child. Because you are a big part in my child’s life… A child that’s
done gone and lets you into his life, like he literally listens to you, he takes characteristics from
you. (27-year-old parent with 2 children in family child care)
A community service provider explains this further:
I believe strongly that the childcare providers in these settings are a very valuable place to receive
this information, because you’re leaving your child here for 8 hours. They’re spending almost the
same amount of time with your child that you are. Almost, not really, but you understand. And it’s
someone that, chances are, is going to have your child from infancy until your child starts pre-K.
So how could you not want that person that is that significantly involved in the development of

Graber 37
your child, to share information, to have information, to give you information that you may not
know exists? (46-year-old community service provider with 15 years of experience in New Haven)
Some parents reported that they consider their child care provider’s advice more relevant than their
health care provider’s advice. For example, a parent said about her child care provider:
She’s like my main resource person, besides me going to the doctors and they telling me what she
should be doing. I’m like, “You’re not even with her every day.” … So I take what [my child care
provider] says, I take that there to heart… I’m glad she’s there and I’m glad I picked that daycare.
(38-year-old parent with one child in family child care)
A community service provider who has worked with child care providers contrasts the role of health
care providers to that of child care providers, specifically around the amount of time they each
spend with the child:
So we have the advantage of forming this very strong long-term relationship with families, where
the credibility is enormous because they see us working with their kids every day… You don’t see
your health care provider very often. So I don’t think they can really count as a support person.
Even though I think that when you visit your health care provider, it’s a very deep relationship.
And people rely on that a lot. But the every day often comes down to us. And really trying to track
what those day in and day out conversations look like, because they’re momentary, but making
sure that they’re… a controlled amount of information that families can handle, and honest at the
same time… So I think that the early childhood teachers and directors are in the real front line.
Because we’ve got these kids all day. (52-year-old community service provider with 13 years of
experience in New Haven)
Further, an early intervention provider described how parents sought advice from child care
providers around specific topics they felt their pediatricians didn’t address well:
I think a lot of daycare providers and parents, unfortunately, don’t access their pediatrician for
things that are not specifically related to immediate illness. Like behavior, like feeding, like
sleeping, so they’re accessing people in the community, family members, and they’re either
thinking, either they haven’t gotten a positive response from the pediatrician when they’ve brought
up these concerns, and the pediatrician said, “Oh, you know, if they get hungry enough they’ll
eat.” Plenty of pediatricians have been dismissive, frankly, of parents’ concerns around things that
take more time and take more in depth kind of assessment than typically you’re going to get at any
sick child visit or even a well child visit. So I think daycare providers and families don’t honestly
think of bringing up this stuff. So if the daycare provider says, “Oh, I used gripe water for my baby
and that was fine,” they go out and they find gripe water and they don’t ask the pediatrician
because the pediatrician says, “No, no, no, they’re just teething, they’re fine, they’ll get over it.”
Well yeah, but if you have a baby that’s been crying for four hours, you know… so I think that has
an impact on what people are going to ask. (Early intervention provider)

Graber 38
Even some health care providers acknowledged the unique role of child care providers, stating how
the child care provider can supplement the health care provider’s clinical assessment. For instance,
a health care provider stated:
I really feel like the child care providers have a better insight than we do as pediatricians, because
they see them more frequently than we do… [If] I don’t think everything’s quite right with this child,
so I just say like, “How is the kid doing in school or in daycare?” “Any comments from the
teachers?” And that will give you a lot of insight. (35-year-old health care provider with 6 years
of experience)
On the other hand, a health care provider working in a community health center countered that the
time spent with child care providers is still limited:
I think that you also have to understand… that even though they have the kid for 5 or 6 hours a
day, that’s still a snapshot - it’s a long snapshot, but it’s still a snapshot - and the child may behave
differently at home. (61-year-old health care provider with 31 years of experience)
A health care provider described a tension between concern over the quality of information that
family child care providers share with families and acknowledgment that child care providers are
accessible to families when they need support:
Because as a provider I say, you should not [give health advice], you should refer them to their
[health care] provider. Because I don’t know what kind of training they’ve had… But, as somebody
from the community, if a parent is picking up their kid at 9 o’clock, I know we’re one of the latest
open clinics -we’re not open anymore… So you look at your resources, what you have, and the
childcare provider is right there. And they’re with your child every day. And they have experience
of other kids. (37-year-old health care provider with 8 years of experience) Another community
service provider furthers this theme, stating that child care is important because this is where
families go on a frequent basis:
[Child care providers] spread the word. And most of them are parents themselves. They meet each
other in school; they meet each other in the church; sometimes they are co-workers. So it’s a
network. And that’s how they operate… Because these are the places that [families] go. (42year-
old with 4 years experience working in New Haven)
B. Child care providers are an extended part of the family support system
In addition to the amount of time child care providers spend with children, many parents said that
they felt like their family child care was an extension of the care they provide their own child at
home. For example, one 46-year-old parent stated, “it’s just a continuation of what I do at home.”
A few participants also remarked that the time child care providers spend with children means that

Graber 39
in some ways child care providers share the responsibilities of parenting. For example, one health
care provider called child care providers “a really effective substitute parent, which is really what
people who have kids 40 hours a week are.” A parent agreed, stating:
It’s for the kid’s sake that the daycare providers have to be like the surrogate parents to try to lay
a foundation for these children that aren’t laid at home. And try to communicate that to the parent;
hopefully [the parents will] take that on and continue it for the benefit of the child. (46year-old
parent with one child in family child care)
Other participants added that child care providers’ sense of closeness with the parents is like family,
which makes it more a relationship where advice is shared. For instance, a 38- year old parent said:
“She takes the kids like they’re her own. So that’s why I trust her with mine.” A community service
provider agreed, but then also added a statement of caution:
They feel like they are part of the family. They feel like, “We are friends, I can [give
advice]”because I’m pretty sure they never ever think about giving advice as a health provider.
You’re giving advice as a friend or a person who cares about you… they do play a very important
role in the family. But they are not the family itself. They can provide information, but they cannot
choose what the family is going to do. So just make them aware that they do have an important
role; yes, they make a difference; and the more educated they are, the better they can do in the job.
(42-year-old community service provider with 4 years of experience in New Haven)
One pediatrician attributed this sense of extension of the family or of the home to the changing
models of family and community. He said:
I think that what has happened is that we no longer have nuclear families, so that we sometimes
don’t have the relationship of having a grandparent or aunt or older adult who could give that
advice. And what has stepped in is, the other adults that would interact with the family, and the
child care provider is part of that interaction. (61-year-old health care provider with 31 years of
experience)
In addition to acting as an extension of the family, several participants reflected that child care
providers can act as a “second set of eyes” for the parents, following the children closely and also
observing behaviors or activities that the parents may not otherwise recognize. For instance, a
parent reflected:
If they are sick, after a couple of days I take them to [my child care provider], she makes sure to
keep an eye on them, and she does, she’ll check their temperature on a regular basis, check their
bowel movements, everything, just to make sure that nothing funny is going on. She does a really
good job on keeping tabs on all of that… She’s really good at paying attention what they like and
what they don’t like and taking notes about it and letting us know… If she sees anything funny or

Graber 40
them acting different, she does let us know right away… She does pay attention to detail when it
comes to their habits and stuff, just to let us know. (31-year-old parent with two children in family
child care)
Another parent agreed:
[I ask my child care provider] about her interactions with him throughout the day, anything that
she may have picked up on or noticed or seen, that I’m missing. Absolutely. (41-year-old parent
with one child in family child care)
C. Child care providers have experience, but not expertise
Parents, health care providers and community service providers all agreed that some family child
care providers have experience with children, their development and their health, but several also
expressed doubt that child care providers have the training or expertise to share specific advice
with families. A pediatrician summarized this conflict:
The whole mantra really has been is the parents see these kids all the time, but they’re not very
medically knowledgeable; I am very medically knowledgeable but I don’t see them much of the
time. But the daycare people and the nurses see these kids a lot of the time and they have a lot of
medical knowledge, or not -- the nurses do, but at least the [child care providers] at least have the
privilege of seeing them and maybe can be educated enough to know when there’s a problem that
needs to have something done, even though they maybe can’t do it. So there’s a real opportunity
there. I think that we probably should be taking greater advantage of that. (59-yearold health care
provider with 29 years of experience)
1. Family child care providers have experience
Parents, some health care providers and community service providers believe that child care
providers have experience with children, allowing parents to trust them to care for their children.
For example, a health care provider trusted the objective experience of her personal child care
provider:
They’re more objective than I am as a mom and a pediatrician. So I really trust this one child care
provider for her health assessments, and the next time [my child] had a mole that she thought was
concerning and looked bigger, so I took him right to the dermatologist. They just have a lot of
experience. It doesn’t matter what their education background [is] but I think experience [means]
a lot for a lot of child care providers. (35-year-old health care provider with 6 years of experience)
A health care provider who works as a medical consultant for various child care centers and homes
acknowledges the experience of child care providers, but wants them to have support in what
information they share with families:

Graber 41
I think it’s really important to work with the [child care] providers because I think they do see
themselves as, some of them, having a lot of experience. And you do want to make sure they’re
passing along the correct information. (61-year-old health care provider with 3 years of
experience)
While health care providers and community service providers reflected more upon family child
care providers’ experience explicitly as child care providers, most parents believed that the
experience of their child care providers came from their dual role as a mature parent. Parents
described their child care provider as “motherly” and one cited that her child care provider is
already functioning as “a mother of four.” For example, one parent described how she felt
empowered and normalized after speaking with her child care provider about her experience as a
parent:
I felt relieved because to know that someone else went through [raising a child] and that my child
isn’t strange or it’s not just a problem with my child, that kids go through these phases; it made me
feel a lot more confident in my parenting skills and to know that just keep going and doing positive
influences and it’ll pass eventually. (27-year-old parent with one child in family child care)
A parent with one child in family child care agrees, expressing that because her child care provider
is a parent, unlike health care providers, she appreciates her advice:
Yeah, because like I said, [my child care provider], she concerned and she knows. She had kids
all her life, forever. Doctors have too, but the majority of them don’t have kids, the majority of
them don’t deal with kids like that besides physicals and going off reading the charts and
everything. They do their research and they look up things. But they don’t have kids. [My child care
provider] have kids, you know what I’m saying, it’s so different. (22-year-old parent with one child
in family child care)
One community service provider believes that parents connect with child care providers not only
because they are also parents, but because they come from the same community or have the same
racial or ethnic background:
So if I have a child at the same age or older, and I’ve been through the same situation, it’s ok for a
Spanish speaker say, “Hey, it happened to me, I tried this, this, and this, so I think you should try
it too.” And most likely, they will. First of all, because it comes from another person from the
same community. (42-year-old community service provider with 4 years of experience in New
Haven)
On the other hand, a mother and father who were interviewed together disagreed on how to reflect
on their child care provider’s credibility as a parent:

Graber 42
Mother: She is a mom. And it’s a little bit of common sense mixed in there, a little bit of mother’s
intuition-
Father: But you also understand, her children are older. She was a mother of small children at a
different time.
Mother: Right. But sneezes, teething, all that still remains the same factor
Father: Not truly, because now we have all different kinds of medicines, vaccinations for smaller
children, that she didn’t have when her children were smaller. And then you also have
certain things, certain bacterias, that wasn’t as opposed to your child as it is now.
2. Doubting the expertise of family child care providers
The parents, health care providers and community service providers interviewed expressed doubt
concerning the expertise of family child care providers, referring to 1) suboptimal quality of child
care, 2) suboptimal quality of health advice, and 3) misinterpreting health care providers’ orders or
immunization standards.
i) Suboptimal quality of child care
Several health care providers and a few community service providers referred to suboptimal quality
child care. For example, a health care provider said:
There are many [child care environments] that are not so wonderful. Like most of the commercial
ones… I take competence seriously. And there’s not a lot of competence in a lot of those places.
They really don’t have the sensitivity. (70-year-old health care provider with 35 years of experience)
A community service provider discussed the limitations of child care by friends and relatives:
So they go [into school] from home childcare by a friend or a relative who may have questionable
levels of education, may not have the mental resources, mental capacities, or physical resources,
to really provide a preschool experience in their home. I’ve gone to homes where children are just
sat in front of the TV - Spanish television, and that’s what they do. (67year-old community service
provider with 47 years of experience in New Haven)
A 51-year-old health care provider with 18 years experience in a community health center agrees,
explaining that child care providers may have inappropriate expectations of children’s
development:
The babysitter says that they’re too active. And then when you say, “So what’s your kid like at
home,” and at home they’re perfectly fine… and then you start asking questions about what
happens at the babysitter’s, well, they’ve got the TV on all the time, and this is a kid who doesn’t
want to sit in front of the TV all the time. So for that babysitter, that kid is too active. (51-yearold
health care provider with 23 years of experience)
ii) Suboptimal quality of health advice

Graber 43
Some participants felt uncomfortable with the quality of health advice given to families. Some in
particular wanted family child care providers to ensure that the information that they were giving
families was the same as their health care provider would give. For example, a health care provider
said:
The other problem is people who have outdated information, information that they really don’t
understand but they feel like they should be sharing…And where we end up being in sort of the
middle between the parent who thinks one thing and the provider who thinks or the grandmother
or whoever who thinks another thing, and we have to sort of mediate. (51-year-old health care
provider with 23 years of experience)
A health care provider stated:
[The idea of child care providers giving health advice] kind of makes me a little nervous, to tell
you the truth, because you don’t know what they’re saying, or if they’re giving the same advice that
you would give. I think the quality of care of childcare providers is such a wide range, I’m sure
some provide excellent care and have been doing it a long time, and then there’d be some who are
a little bit newer or younger and don’t know quite as much, or aren’t as informed. So I would be a
little bit wary of taking medical advice from a [child care] provider… But in terms of telling them
to take Tylenol or Motrin or anything like that, I would want them probably to check with a medical
provider to see if that’s accurate advice. (34-year-old health care provider with
1.5 years of experience)
Further, one of the early intervention service providers said that although well intentioned, child
care providers may not be giving the same advice as a pediatrician:
So I’ve seen a lot of [child care providers give] advice… “I told her she didn’t need that,” or “She
can stop doing that,” or just, “Try this” - really good intent behind it. But I don’t think probably
in line with what the pediatrician would recommend.
Another early intervention provider agreed, adding:
In the particular instances that I’m thinking of, I don’t know that it’s necessarily a barrier, or if it’s
the childcare provider’s intent to help the family they care about. “This worked, I did this with my
child and it was fine.” “So-and-so, I did this with my child, or I know somebody that did this, and
that’s how they gained weight,” or “that’s when they started to sleep through the night,” or “they
didn’t choke on that at all,” … I don’t think it’s a slam against the pediatrician, I don’t think it’s an
attempt to overstep them, I think it’s a legitimate attempt to help them, and they just maybe think
very highly of their own skills or ideas that they feel like they’re appropriate to be shared, and
they’re not always.
A health care provider did not feel child care providers had more expertise than lay people:

Graber 44
Daycare workers, I don’t have a sense that they’re overly [qualified] - not any more than
grandmothers, and next door neighbors, and your best friend, or the internet. (60-year-old health
care provider with 32 years of experience)
One parent felt that his child care provider had a good understanding of what’s going on within her
child care, but little grounded knowledge in children’s health and development:
You know the situation of how everything [works in your child care]- I understand that. But you
ain’t know nothing. This wasn’t discussed between you, or between us, like you just come out and
just say [your thoughts on development], “What do you base that on?” (27-year-old parent with 2
children in family child care)
iii) Misinterpreting health care providers’ orders or immunization standards
Several parents, health care providers and community service providers recalled experiences where
child care providers had not understood immunization guidelines or medication administration
instructions appropriately, and then inappropriately advised the parents.
For example, a parent recalled:
I remember one time showing her the medications that he was on at the time - at the time he was
on a steroid, a liquid steroid, and just had a really, really bad time with the croup. And she wasn’t
necessarily adhering to the medication schedule. Which is key and important, especially with
breathing issues… if you can’t do this during the time that he’s in your care, then I need to know
that, so that I can arrange to get here when he needs the medication. But it’s important that he
does get it when he needs it. (41-year-old parent one child in family child care)
A health care provider felt child care providers were inappropriately informed about vaccination
requirements, and in turn misled families:
One family… said that their childcare provider, on December 11th, did not allow her child to
continue to go to their program, because she didn’t have the flu shot… I couldn’t understand - I
remember that was a phone call that I did to a childcare provider, “Why on December 11th did you
tell mom that she couldn’t go back?” “Because she needs a flu shot, she needs a flu shot.” And I
said, “But that’s not til January 1st. She’s got at least 3 more weeks that we could try talk to her,
but in the meantime mom can’t go to work, and the baby’s at home and is not going to your
program!” And on top of that, they were making her pay, to hold the slot! That I thought was
scandalous. (37-year-old health care provider with 8 years of experience)
Another health care provider said that while he relies on child care providers to tell parents about
immunization, they can misinterpret the recommendations:
You have to rely on the daycare providers, and they get these [Department of Public Health]
bulletins too… Now they don’t always read it carefully, and we had a number of kids who were
being told that they had to have a Hep A vaccine when they weren’t old enough to be getting a Hep
A vaccine. (59-year-old health care provider with 29 years of experience)

Graber 45
One parent, however, had an opposite experience, where the health care providers did not know the
appropriate immunization schedule, and had to be informed by the nurse affiliated with the school
or child care:
Sometimes, it happens a lot with my son and a couple of times with [my daughter], when the school
nurse or the daycare nurse, they send a message that he has or she has to have this shot in a couple
of months… I called the hospital and the hospital says that he don’t need it; he didn’t reach such-
and-such yet. So I went to talk to the school. I explained that they said. She told me that they don’t
know what they are doing. She went, she brought a book, and she printed 2 or 3 pages from that
book… and gave it to me… In the next week I had an appointment with the doctor, so when I went,
I explained, she said, the doctor again, she said, “You don’t have to take this immunization. This
is not correct.” So I showed her the paper - this is what the nurse is saying. And the doctor read
the paper and said, “Ok, the nurses know what she’s talking about so we’ll give him this
immunization.” So the school nurse knew better than the hospital in that point. (31-year-old parent
with one child in family child care)
D. Child care providers help bring children into regular well care
Health care providers and parents largely agreed that family child care providers help encourage
families to get frequent well child care and required vaccinations. For instance, a health care
provider said:
I think they can reinforce the importance of making sure that the children are going to the doctor’s
and keeping up their regular well-child appointments and their immunizations. I think that’s still
an area that the [child care] providers are a little bit uncomfortable with, because I think
understand the immunization records and the physicals is difficult. [sic] (61-year-old health care
provider with 3 years of experience)
Parents expressed satisfaction when their child care provider informed them about upcoming
appointments or vaccines. For example, one parent said she receives regular reminders from her
child care provider:
Yeah, she’s always given us the fliers. The nurse comes in to check up on the kids, and she’s like,
“Here’s the latest flier, and these are your child’s coming up [shots], that they need.” We usually
already have the information, but she does let us know. (31-year-old parent with 2 children in
family child care)
One health care provider believes that the system of unannounced inspections for licensed child
care providers motivates child care providers to facilitate getting children into their health care
provider:

Graber 46
So the licensed providers supposedly get inspected and visited and if their paperwork isn’t lined
up, then they’re out of business. So they have an incentive to have everything happen when it’s
supposed to happen. It’s their livelihood that’s on the line, so of course they’re going to push for
that. Are there other things? Those kids get their well baby care, as a group I think they get their
well baby care and their shots maybe in a more timely fashion than some other people for whom it
doesn’t matter as much. (51-year-old health care provider with 23 years of experience)
An early intervention provider from the focus group agreed, saying that children who enter child
care are more likely to get vaccines and go to well child visits:
Another positive is that when they do attend daycare they have to have their shots up to date and
things like that, and that’s one thing some of the kids that I had seen, they were missing their
pediatric appointments, but once they started daycare, all of a sudden they were on target. This
particular daycare was even sending home notes to remind them when to go to the doctor. So that
actually was really helpful that way. Because I’m not sure that if they were staying home that these
appointments would have been kept.
One health care provider says she’s “grateful” when a family comes in with a health form from a
child care provider: “I’m usually grateful, because they may have otherwise not received [well
child care].” A health care provider said that she learned about the new influenza vaccine
regulations for children in child care from her patients, who came in with notes from their child
care providers:
The daycare, telling me that I need to do it. And a lot of parents are coming in, “Oh, the daycare
said I had to do this.” That’s kind of how I learn about those things. (35-year-old health care
provider with 6 years of experience)
IV. The Role of Communication
Issues of communication were a common thread through all the interviews, especially
communication between parents and family child care providers. Four primary themes emerged
from the interviews: a) Frequent and consistent communication between a parent and the family
child care provider helps build trust, b) Conversations between child care providers and parents
regarding concerns about children is challenging, c) Conversations between health care providers
and child care providers are limited due to concerns about confidentiality, and d) Suggested
strategies to improve communication between child care providers and parents.

Graber 47
A. Frequent and consistent communication between parents and child care
providers builds trust
Parents reflected that they appreciated speaking regularly with their child care providers, especially
about non-urgent issues, so that they knew that their child was well cared for. For instance, a parent
said that her child care provider “keeps us connected and informed of what [the children are]
experiencing each day.” A parent said that she initially was anxious when she heard from the child
care provider, thinking it meant something was wrong, but then realized that it afforded her the
opportunity to partner with her child care provider in the care of her daughter:
I get phone calls, even though I’m nervous or whatever, it don’t even be nothing major. She’s just
informing me about something. If [my child] mess in her clothes, she’ll call me like you know,
“I’m changing [your child] into some clothes because she messed herself” or whatever. That stuff
right there - it might be a reminder to other people, that it’s like, oh, ok, so I know to put another
pair of clothes in the bag, but she she’s older than me, I guess I was just blessed, because she
informs me, she supports whatever I’m trying to do with [my child]. (38-year-old parent with one
child in family child care)
A parent routinely calls her child care provider to check in on her son:
Me and [my child care provider’s] relationship pretty good. I call her sometime, ask her how he
doing, is he ok, is he interacting, did he take a nap, did he eat today, because he’s funny. Sometime
he won’t eat, sometime he will eat. She answers my questions real good. If something ain’t right,
if she see something, even a small thing like lotion or whatever, she even goes out of her way to get
certain lotions and stuff for the kids. (41-year-old parent with one child in family child care)
Other parents reflected that this regular communication was especially helpful when their children
were sick. For example, a parent said:
When I feel that [my child’s] not feeling well, I let [our child care provider] knows and [our child
care provider] just like keep an eye on her. When I pick her up, she said, “she was fine, she was
like a little bit sleepy today,” so she just keep an eye to let me know what was going on during the
day with her, so I know exactly that she’s getting better or she’s getting worse, or just nothing. (31-
year-old parent with one child in family child care)
Another parent agrees, saying that medications are helpful for her son, but that regular
communication with her child care provider is more beneficial:
But I have to say that in the last year and a half he hasn’t had any issues with croup. And I know
it’s because of the reflux medication and keeping on that, but just also again the fact that she’s -
we’re in contact throughout the day, whether it’s text messaging or whatever it is, if there’s an issue
or if she has a concern or a worry, she’s on the phone. She’ll call me. (41-year-old parent with one
child in family child care)

Graber 48
Community service providers reflected that they believed that these conversations between parents
and child care providers about daily concerns and events laid the groundwork of a trusting
relationship that serves as a basis from which to act when real concerns arise. One community
service provider thinks that providers who routinely talk about normal child development will be
better equipped to assist families if there is a developmental concern:
I think there should be some education and reliance on those providers to talk about normal child
development, developing a trusting relationship with the family so that if they do have concerns -
and then to know the referral network and where to send them. (52-year-old community service
provider with 18 years of experience in New Haven)
B. Discussing child care provider concerns with parents
When child care providers have concerns about children, parents, health care providers and
community service providers agree that communication becomes especially critical. A few parents
and community service providers expressed frustration with how concerns were addressed by child
care providers. Several offered ideas of what could improve communication, understanding that
communication around sensitive issues is difficult.
1. Unhelpful communication
One parent reflected her frustrations when her child care provider told her about her son’s possible
developmental delay at drop-off time:
I dropped the children off in the morning, and [my child care provider] said something about - oh,
she was telling me to get on the ball about school. This was months back. And I was like, you’re
completely right. I need to do that. And then I said, “Yeah, because I’m going to try and look for
an all-day program.” And she was like, “I don’t think he’ll last all day. I’m like, “What the heck
is this. He lasts all day here. I don’t understand that.” And she was like, “Well I had a
conversation with the nurse. And we don’t see him keeping up to par with a classroom of 15 or
more.” And I’m looking at her like, you’re pretty much telling me - I mean, there was other
verbiage in that... But it came off to me that you were telling me that my child is slow. Where he’s
not on a 3 - oh, she told me, “he’s not on a 3-year old level.” Those were her exact words. (27-
year-old parent with 2 children in family child care)
This same parent additionally felt that she was being talked down to by her child care provider,
further stressing their relationship:

Graber 49
But we’ve had some instances where it’s just like, Why is she talking to me like I’m 15? And I am
27 years old. And my oldest child is 3. I had children as an adult. So sometimes I’m just like I
don’t understand why she feels she can be that loose talking to me. (27-year-old parent with 2
children in family child care)
A community service provider stated that she understands that it’s easier to lay blame for a behavior
on children and parents instead of being more reflective:
[T]hey need to be able to talk to parents, but do they understand what they’re talking to parents
about? And the easiest thing to do when a kid is sort of off the wall is to pathologize the kid and
the family. That’s the easiest way to deal with it. The hardest thing to do is to say, “What could I
do differently? What could we do differently?” (63-year-old community service provider with 18
years of experience in New Haven)
2. Helpful communication
Both in anticipation of difficult conversations and prior experiences with them, parents, health care
providers and community service providers offered suggestions about how child care providers
could communicate more sensitively with parents. This included how to phrase concerns, how to
establish a comfortable environment, and how to provide support and partnership going forward.
For example, one community service provider said that child care providers need to be thoughtful
in how to phrase concerns:
Perfect example: potty training… I know you can be very tactful. “I don’t know if you started potty
training at home yet? But let me tell you, he’s doing a wonderful job here, he’s excited about it.”
I would like that. I wouldn’t say, “Why is your kid still in diapers?” And some people do! So it’s
kind of touchy, as a parent giving another parent [advice]. (46-year-old community service
provider with 15 years of experience in New Haven)
One parent wanted suggestions about how to address the concern about his son immediately, not
only to learn about the concern:
You really got to handle it the right - with silk gloves. You really got to handle that very gently.
You got to sit down… A situation like that, you have to come up with the problem and the solution,
right away. The simple fact is, to tell them the problem, you tell them the solution to calm down.
You just can’t say, “Well your son’s a little behind.” “What’s going on? What do you mean behind?”
Now you have to defuse the situation with, “He’s a little behind. This is what methods that we can
do together to put him on the right page.” You just told them something but then you also gave
them a solution so now they’re not as upset. Now they’re concerned. “Oh yeah, what can we do?”
“Well, actually you read to him a little bit more, or such and such a little bit more, or pretty much
just articulate to him a lot more, and I’ll do the same here, and see if we can see changes over a
couple of weeks.” And now you have the parent on board, because the way you present the problem

Graber 50
is not saying, “You got a problem,” and then walking away. (27-year-old parent with 2 children in
family child care)
This same parent equated communication with love and partnering to care for the child:
I want you to care for my child like it’s your child. I want you to show me that love - that right
there builds a communication between me, between you, and between my child. Because now I
know where my child is, I know what needs to be done, and I know what we’re doing. Because
we’re both have part in raising my child. Because while I’m at work, you’re raising him. (27year-
old parent with 2 children in family child care)
C. Conversations between health care providers and child care providers are
limited due to concerns about confidentiality
Health care providers expressed concern about speaking with family child care providers because
they wanted to uphold patient confidentiality and the Health Information Portability and
Accountability Act (HIPAA) legislation. For instance, a health care provider said that she has to be
cautious about what health information she shares, although she acknowledged that child care
providers could also have a signed release from the family:
With the school nurse, the parent can sign a release or something. I guess technically they could
probably do that with a childcare provider too. With a school nurse, they’re a medical professional,
so you feel you can speak on a medical level with them, and often they do have that in place where
the parents have released the authorization for you to give them the medical information, so you
feel like you have that protection, so that sort of helps… You have to think about HIPAA. You have
to be cautious about what you’re saying about the child, and how the mother or father would feel
about it. So that’s probably the biggest thing that we have to be cautious of, because we don’t want
to violate anybody’s confidentiality. So we have to be cautious with that. And you can listen to
what the childcare provider has to say, but I think we’re so limited as to what we can share, that
sometimes it makes it difficult. (34-year-old health care provider with 1.5 years of experience)
A community service provider believes that this is a large enough hurdle that child care providers
will not have access to health care providers:
I’m not sure whether I were aware of whether childcare providers actually have access to medical
providers [sic]. I would think that the rules of the road are very similar to what ours are, that you
just can’t take liberties in contacting medical providers unless the family wants you to do that on
their behalf. So I think that that may be a relevant factor to how involved they can be. (62-year-
old community service provider with 35 years of experience in New Haven)
Some parents said that they did not want their child care provider to know everything about their
child’s health history. A parent said:

Graber 51
We’re talking about [my child care provider] and my pediatrician being on the same page
healthwise?… What’s the information that’s going to be passed? Because… certain things, that I
wouldn’t like my kids – you know, my kids’ business from my doctor’s, to be out there… But it all
depends. Certain things that you discuss with the pediatrician you don’t want to discuss with
anybody else. (27-year-old parent with 2 children in family child care)
Members of the early intervention provider focus group agreed that families are sometimes guarded
about the diagnosis and services that a parent receives, even when they are working within a family
child care:
Participant 1: That’s often, that the parents have not told the daycare what the diagnosis is.
Participant 2: Sometimes for fear that their child may not be able to stay there.
Participant 3: They don’t want to be treated any differently.
Participant 1: Or they haven’t told other people. (Several voices: Right.) I had a daycare… with
two contact sheets. I’d leave one for the parent that I would put in a sealed envelope, and
the other would just be suggestions, that mom also got a copy of, for just the daycare time.
So it depends on what that family, like you said, some can be very sensitive about what’s
said. And they just want to see it all, so.
D. Suggested strategies to improve communication between child care providers
and parents
Parents and community service providers emphasized the importance of strong communication
between child care providers and families, especially when communicating about concerns. A
parent recalled a time when she was frustrated with how her child care provider communicated
about concerns over her son’s development and how she would have preferred being approached:
It’s all on verbiage [sic]. If I’m grabbing the diaper bag about to head out the door and you tell
me that you think my child is not on a 3-year old level, it’s extremely unprofessional. As a daycare
provider, as just a parent. Because you would not want to be approached in that same manner. If
you tell me, “If you have some free time, I’d like to talk to you about [your son]’s progression,”
I’m going to take you seriously and professionally. (27-year-old parent with 2 children in family
child care)
A health care provider mirrored this concern and focused on how to create the right environment
to discuss concerns:
I think some of the things that we talk about is, they come up with some of these [concerns]
themselves, but setting up a time when they can talk with the parent when it’s not pick up or drop
off. Because I think that’s a problem if they’re trying to come across to the parent when the child’s
being picked up and wants to go home, and the parent wants to go home. (61-year-old health care
provider with 3 years of experience)

Graber 52
A community service provider who trains family child care providers felt that knowledge empowers
child care providers to have the difficult conversations with parents and then to connect them with
the services that they need. Speaking about family child care providers who have gone through
training, he said:
Home childcare providers have shared with their parents that they have observed the behavior of
their preschooler who is under their charge, and they don’t know what it is, but they say to the
parents, “Look, you have a right,” because they have been trained. “You have a right to request
that the teachers and the school administrator get together and work with you to find out exactly
what could be wrong.” They’re giving out the information to parents to seek help, and that is
valuable. (67-year-old community service provider with 47 years of experience)
A community service provider felt that training that emphasized how to phrase difficult discussions
would be of benefit to the relationship between the child care provider and the family:
But in an attempt to insure the best care for the child, they should be tactful in their approach on
how they’re obtaining the answers that they’re looking for, like I don’t know, “Well what’s going
on? Billy’s been acting out. So, what’s going on at home?” What does that mean? Or it’s just a
different approach. “We didn’t have such a good day today, and things have been pretty much the
same here. We have a schedule that we go by daily, and it really doesn’t alter too much from that.
So I’m curious, are there any changes at home that may be…” You know, not “What’s going on?”
(46-year-old community service provider with 15 years of experience in New Haven)
A community service provider models effective discussion with parents so as to not undermine the
role of the health care provider:
“[The health care providers] think that they want to put tubes in [my child’s ears]. What do you
think about that?” Because it’s a big step. And we’ll say, “Tell me what they’re saying first.” My
first thing is to always ask another question. I don’t want to leap into the fray, because I don’t want
to be in a battle with a pediatrician. “What are they telling you?” “Well, they’re telling us that
she has fluid in her ears all the time.” I’m going, “Ok.” “Well have you ever heard of that?”
“Actually that does seem like the best reason to get tubes, because here’s what life sounds like to
them, and here’s what’s going to happen to their language.” (63-year-old community service
provider with 18 years of experience in New Haven)
V. The Role of Personal Relationships
When reflecting on communication, parents, health care providers and community service
providers all agreed that having personal relationships, knowing and trusting someone, increased
the quality and quantity of information sharing. Three prominent themes emerged, including a)
families listen to the people with whom they have personal relationships, b) child care providers

Graber 53
do not communicate with health care providers because they do not have relationships with them,
and c) health care providers communicate only with social service agencies with whom they have
relationships.
A. Families listen to the people with whom they have personal relationships Parents,
health care providers, and community service providers all agreed that personal relationships not
only allow for ease of referral and communication, but that families are more likely to listen to the
people that they know and with whom they have a personal relationship. For example, a community
service provider said, reflecting on her own experience as a parent:
If my sister tells me that I need to do something, I really listen very closely. If my childcare provider
woman says, “Jeez, [your daughter’s] looking like she’s very anxious and I’m really worried about
her,” I take that very seriously, because she sees this child every day. The depth of the relationship
I have with the person is the person I’m going to really listen to closely. (52year-old community
service provider with 28 years of experience in New Haven)
Additionally, a health care provider acknowledged the great diversity of thought and beliefs in our
country and that ultimately people listen to the people that they respect:
You’re talking about a very complicated group of people in this country. You’re not going find
people universally respect anything, whether it be the president or a doctor or the health
department or the internet. You’re just not going to find people in agreement. And that depends
on who their guru is. (60-year-old health care provider with 32 years of experience)
One health care provider valued the relationships that child care providers have with parents over
her own expertise. She said:
I really think as long as [the child care provider] relaying the [health] information understands
what they’re supposed to be gathering… I think it’s easier if it’s someone the parent has a
relationship with… I haven’t met that many of the parents, so I think it’s very difficult for me to hop
on the phone and say, “Such-and-such did such-and-such type of thing.” I’m an unknown. So I
think there’s that whole thing about working with parents, it really needs to be someone that the
parent’s familiar with and has some kind of relationship with. (61-year-old health care provider
with 3 years of experience)
Another community service provider who works closely with child care providers said that families
begin to trust child care providers as they develop a longitudinal relationship over time, showing
their continued commitment to the children and their health:

Graber 54
But remember, we have families often from the day the kids are born, until they’re graduating. So
we have the advantage of forming this very strong long-term relationship with families, where the
credibility is enormous because they see us working with their kids every day, and we work closely
enough with the pediatricians and we’ve been around long enough that we know a lot of the
pediatricians and so we can sort of help with that. (63-year-old with 18 years of experience in New
Haven)
B. Child care providers and health care providers do not communicate because they
do not have personal relationships
Health care providers largely asserted that child care providers and health care providers do not
collaborate or communicate because they do not know each other or have personal relationships.
For example, a health care provider said that child care providers are not only unlikely to call
because they do not know each other, but that they need a relationship in order to adequately address
their questions:
How do you make these relationships? And I think it’s simply that if people feel like they know you
and can call, they will, and if they don’t know you, they’re not going to call. So, I think that’s
primarily the issue. And I also think that because of the nature of the issues that come up, they’re
very complicated, they’re generally not a straight forward question about bedbugs, or if someone
has a cold or a fever and they need to go home… But I think the complicated questions about
relationships and how you foster relationships with families so that you’re able to talk about these
complicated issues is a longer conversation, and it really requires time and trust, and a relationship
there too. And that’s sort of not the world that we all work in. So I think that’s probably the biggest
barrier. And part of it too is that I think it’s hard to identify that that’s the issue. (45-year-old health
care provider with 16 years of experience)
Another health care provider agreed that personal relationships would improve collaboration with
child care providers, but also alluded to their role (or lack of role) as colleagues:
I think that the problem [is] not having a personal relationship with the [child care] provider, so
you don’t see them as colleagues or friends, someone that -- not having a personal relationship.
(61-year-old health care provider with 31 years of experience)
Additionally, a third health care provider stated that because child care providers vary in quality,
he only connects with those that he knows has “competence:”
I tend to refer to a very limited range of people or agencies that I know… You’re talking about a
childcare provider as something as broad as like a nursery school or a daycare center… Of course
I talk to them. But the only ones I’ll talk to normally are the ones where I have some sense of their
competence. If it’s one of the proprietary ones, I’m not likely to call… But anyway, so the answer
is that mostly, how do I know, I guess mostly if it’s a place that I’m not familiar with or a caretaker
system that I’m not familiar with, I’ll mostly just try to get the information from the parents. (70-
year-old with 35 years of experience)

Graber 55
C. Health care providers collaborate with the community service agencies with
whom they have personal relationships
Health care providers and community service providers generally agreed that they tended to use
and refer to the community agencies with which they were most familiar or with whom they were
co-located (sharing space on the same premises). For example, a health care provider said:
The resources that you have personal contact with, where you know you can get someone there, or
you know you can at least call and get an opinion from somebody, those are the resources that you
tend to use the most. (51-year-old health care provider with 23 years of experience)
A community service provider said that her work relies on her relationship with health care
providers and that they can depend on her to reliably take care of their patients:
I think that’s what worked so successfully with my program… is the doctors know, I’m the one
who’s doing the calling for their patients. I have to have people with me if I’m doing a home visit
or any of those things, but I’m the one who’s calling their patient, and I’m the one who’s writing
up the reports to go back to them. So I’m like, here I am, you know me, and you know I’ll give you
everything I have. (52-year-old community service provider with 28 years of experience in New
Haven)
A community service provider reflected that having a personal relationship with health care
providers allowed them to fully understand her role in servicing families, furthering their
collaboration:
These are [health care] providers that work with us on a daily basis in terms of, they know we’re
going into the homes with these kids, and so they’re using us as well to get the messages across
that they need. And giving us that [health] information firsthand, as soon as they get it. (41-yearold
community service provider)
A health care provider said that it is much easier to connect families to social services and referrals
if she directly connects them to someone she knows:
It’s really hard to connect people to other services. One thing that’s helpful is just to know the
people really well who are providing the services… Because when we’ve had someone come over
from Clifford Beers, for example, and be here in the building and be able to meet the person in the
room, it’s made a big difference, for people then to follow up with that appointment, because they
feel connected. It’s just like an introduction… So, that’s been, I guess, the main thing that’s been
helpful, is to have a relationship with people and know who they are - the actual person. (45-year-
old health care provider with 16 years of experience)

Graber 56
One community service provider said that she believes part of pediatric practice should be
developing relationships with child care providers:
I think every pediatrician should visit the daycare centers in town, the home childcare centers,
once, at least, so that there is a relationship. (63-year-old community service provider with 18
years of experience in New Haven)
While a couple of health care providers listed several agencies and organizations where they had
contacts, child care providers were not among them. For example, one health care provider credits
his years in New Haven for his interconnectedness:
Granted, I’m in kind of a unique position, because… I know all the school nurses, and all the
people in all the school-based clinics. So certainly can help with a lot of those things… So we sort
of have an in with a lot of these people. And if somebody comes to us with a problem, we know who
to talk to, and they know who we are. (59-year-old health care provider with 29 years of experience)
Several health care providers said that they collaborated frequently with the organizations that were
located on the same premises. For example, one health care provider spoke about having CCCC
(the Coordinating Council for Children in Crisis, a case coordination program for children with
special health care needs) coming to her clinic on a regular basis, enabling their collaboration:
I think in the last six months, we started getting CCCC involved… And it’s really nice we have them
here in-house two afternoons a week, which is really helpful to have them here when these patients
[with special health care needs] come in… so it’s been incredibly helpful, the CCCC, just the
coordination of care there significantly improved the quality of [our patient’s] health, as well as
the relationship that mom had with us and with the school. (34-year-old health care provider with
1.5 years of experience)
Another health care provider agreed that having a co-located agency helped more effectively
connect families into the services that they needed:
We used to have a Clifford Beers worker here that we could actually refer, and she would see them
immediately, practically, that same week, which for mental health is pretty immediate. (37year-old
health care provider with 8 years of experience)
One health care provider spoke about a relationship between institutions, instead of individuals, as
helping connect health care providers and social service providers:
So the nice thing about working in a neighborhood, in a community health center and a
neighborhood health center, is that even if you don’t know the institution personally, the institution
knows our institution, so if someone says they’re calling from here, they at least know that we exist,

Graber 57
so it doesn’t matter so much who the actual person is who calls, it’s just the fact that the institution
is calling. (51-year-old health care provider with 23 years of experience)
VI. Ways for Family Child Care Providers to Achieve Best Practice as Health
Educators and Advocates
Throughout the interviews, parents, health care providers and community service providers
described experiences where child care providers shared or could have shared health information
and advocated for families effectively. In addition to specific health and well-being topics that they
felt were appropriate for child care providers to discuss, the interview participants also identified
methods and techniques that they could use to reach families better. Five main themes emerged
around how child care providers could achieve best practice as health educators and advocates,
including a) an appropriate scope of health advice for family child care providers, b) training and
standardization for family child care providers, c) modeling a healthy environment and facilitating
change for families at home, d) shared and repeated messaging, and e) role definition and knowing
personal limits.
A. Scope of health advice for family child care providers
When asked about what type of advice is appropriate for family child care providers to share with
families, many interview participants responded with specific examples. While all
Table 8. Scope of health advice for family child
care providers endorsed by participants
Health education topics identified:
• Early childhood development, milestones,
and behavior
• Nutrition and healthy eating
• Hygiene
• Oral health
• “Timely health information,” including
vaccine changes and medication recalls
• Mental health
• Medication administration
• Exercise & physical activity
• Health insurance access
• Asthma
participants generally agreed that the
scope of advice provided by family
child care providers should be limited to
specific topics (as discussed further in
next section on training for child care
providers), there was debate about what
these topics would include. Table 8
shows the health education topics that
were suggested by interview

Graber
58
participants as appropriate topics for child care providers to share with families.
Commonly identified health topics
1. Early childhood development and behavior
Many participants felt that child care providers should be comfortable with child development,
both to be able to support children in reaching their milestones with appropriate activities and also
to identify children who are of concern. For example, a community service provider said that she
thought child care providers should know:
Definitely all of the early childhood development. I don’t know if it’s ages and stages or the same
trainings, the same modules or whatever of information that’s given from Birth to 3. And because
typically when you put your child in daycare, your child is going to be there until it’s time to
transition into school... It’s just another person that’s integrally involved with the care of your
child. So ok, when you first brought him here, at say 3 months old, now he’s a year old; there are
other children - just what milestones to look for, between the ages of birth to 3. (46year-old
community service provider with 15 years of experience in New Haven)
A parent said that he would like to know about the developmental stages, does not feel that he gets
that information from his health care provider, and would like to get this from the child care
provider:
The thing that I would like is the development stages like because things I just would like to know,
even though the doctor would tell me, I just want to know sometimes. He has a lot of patients. He
may not – I just want to know what to expect. So having the thing where [he] is where he’s supposed
to be at, this is what he’s supposed to be doing, the weight for a demographic ages, things that
[my child care provider] just give me so I should know… I just feel like there should be a progress
report every month. I believe that it’s a village it takes to raise a child. If I’m on your lesson plan
- I have the same books that you have; like say you’re reading and you started reading this book,
ok, that’s the week that I’ll read this book. (27-yearold parent with 2 children in family child care)
A community service provider thought that this knowledge was important for child care providers
so that they could then communicate concerns to parents and assist them in getting the services
that they need:
So I think there should be some education and reliance on those [child care] providers to talk
about normal child development, developing a trusting relationship with the family so that if they

Graber
59
do have concerns - and then to know the referral network and where to send them. (52-year-old
community service provider with 18 years of experience in New Haven)
A health care provider echoed this same sentiment:
They should know what normal is. They should know what the range of normal is. So that they
know what to worry about, and they shouldn’t worry themselves worrying about things that they
don’t need to worry about. Just sort of basic child development, basic nutrition, basic behavior.
And then if they see something that makes them uncomfortable, they should feel like they can
mention it to the parents. (51-year-old health care provider with 23 years of experience)
2. Nutrition and healthy eating
Parents, health care providers and community service providers across the board shared that they
thought child care providers could influence the eating habits of children by providing healthy
foods during the day and modeling healthy eating for families. One parent said that she receiving
nutrition information from her child care provider, which she then began using at home:
I trust [my child care provider], because she gives me a lot of information… what you need to be
doing with your child. She also gave me a nutrition thing also I think the nurse had left for her,
and I used that, like what type of foods they should be eating, and the portions and stuff like that?
So I try to use that at home with [my child]. She’s like my main resource person. (38-yearold parent
with one child in family child care)
A community service provider said that she thought exercising and nutrition was a good place to
start for health messaging:
I also just think in terms of talking about, this is when children are a little bit older but, exercising,
proper nutrition - we see so many families with kids that have come to - in their home where they
have soda in their baby bottles. Certainly that’s something that as soon as you see it, anybody
should be able to provide a key message. (51-year-old community service provider with 5 years
of experience in New Haven)
3. Hygiene
Hygiene, encompassing handwashing, food preparation, and covering mouths when sneezing or
coughing, was another common theme shared by interview participants. A health care provider
said:
I think things have to be kind of pegged to the level of the audience that you’re talking about.
Settings like that are particularly good for talking about issues of hygiene, handwashing, and
things like that. (59-year-old health care provider with 29 years of experience)

Graber
60
A parent agreed that good hygiene was a way her child care provider was keeping her children
healthy:
Good hygiene practices, washing of the hands every time they come in from outside or touch
anything unsanitary, that type of thing. Wearing the gloves when changing and stuff. Keeping the
place clean. And teaching them also how to start with hygiene, teaching them good hygiene skills
right now. (46-year-old parent with one child in family child care)
4. Oral health
As several child care providers had children brush their teeth during the day, parents and health
care providers found this to be strong modeling and messaging to the family. A health care provider
said that:
I think the oral health is a good place… But I know [one of the child care providers] spends a lot
of time working with the parents, so I took them these informational sheets about different things
like weaning the baby off the bottle or the breast, and so there was a lot of different information
in there that was appropriate for different ages, so I thought as different things came up, they could
maybe put that correct information in there?... I kind of see the oral health as a lead-in to nutrition
about, this is what’s best about the teeth, and not eating this or eating that in a small amount, and
I think that can kind of help with that. I really think they can work with the parents as far as
encouraging them, as the children get a year old, to get off the bottle, and make some comments
about that. (61-year-old health care provider with 3 years of experience)
5. “Timely health information”
New vaccines, medication recalls, and changes in safety standards rarely coincide with a child’s
well child check with their health care provider. Participating parents and community service
providers thought it was appropriate for child care providers to share this “timely information”
with families. A community service provider said that she thought it was important for child care
providers to help families learn about the flu vaccine and to keep their families on track:
The flu vaccine is a good issue. So is the goal that every kid gets the flu vaccine before Dec. 31 of
every year? I know we have a daycare requirement. But one of the things about the daycare
requirement that we’ve discovered is that because there are follow-up visits that you have to do
for some of these immunizations, that keeping track of that flu vaccine thing became very hard,
very sticky, because parents already submitted their PE form, and then they ran in to get whatever,
or they didn’t, for a follow-up vaccine. (63-year-old community service provider with 18 years of
experience in New Haven)

Graber
61
One parent was frustrated that she did not hear about Tylenol recalls from her health care provider,
but was relieved to hear about it from her child care provider:
Just like, one thing [my child care provider] did inform me about, the Tylenol that was taken off
[the market] - my doctor did not tell me that. And [my child care provider] told me that. And I was
like, “What -- I just gave her a Tylenol,” and she was like, “Don’t panic, don’t panic. They just
took it off the shelf.” She was like, “How old is your Tylenol? Look at the expiration date and
everything.” You know, something like that, that should be in the mail from your doctor, or your
doctor should be calling you and informing you. She informed me about that… it’s like that’s the
person I go to. (38-year-old parent with one child in family child care)
6. Mental health
Parents and community service providers felt that family child care providers were in a good
position to offer guidance about mental health. One parent said that he would turn to his child care
provider for advice, particularly because it is so difficult to access his health care provider:
Maybe if I am worried about my children like maybe mental health? If I was concerned about
something, if they wasn’t growing up as fast as other children, I may ask such questions. Especially
that it took forever like, normally just like if you go to the hospital every six months just for
checkup, so if there is such concern, I’m definitely may talk to [our child care provider] and see if
she can like help me with that. (31-year-old parent with one child in family child care)
A community service provider believed that training of family child care providers in recognizing
symptoms of mental health disorders in children would better their lives and enable their open
communication with parents:
I hope actually that [mental health training for child care providers] brings the children into a
world where adversity is not tolerated and that kids and families can live safer and with less
stress… So for the [child] care providers, I hope it creates an awareness and an understanding
and a confidence in being able to address it or at least engage in conversations with parents
around it… Helping them understand their own experiences helps them then help other people.
(52-year-old community service provider with 18 years of experience in New Haven)
7. Medication administration
Several parents found comfort in the fact that their child care provider was trained in medication
administration. One parent described her reaction to this knowledge:
[The child care provider] said, “You know, I have my license if you need me to give her
medication,” so that was also comforting because I wouldn’t even send it, because I’m like, “What
if she give the wrong doses? Or maybe she’s not comfortable giving [my child] this because she

Graber
62
don’t want to be responsible,” but she made me so comfortable, and so I was able to just send the
medicine, and she was like, “Ok, as long as it has the dosage and everything else,” she was fine.
I like the fact that - because I know you said is there any other daycare - and like, “We’re not
doing that. Unless we have a nurse here. “So my child have to go home then. And I miss days out
of work. (38-year-old parent with one child in family child care)
8. Exercise & Physical Activity
Parents appreciated it when their child care provider kept their children active and exercising
throughout the day. When asked how his child care provider kept his children healthy, one parent
responded:
Activity. She keeps our kids active. With the other kids, they interact, they’re constantly doing
something, she just don’t sit down at a desk and watch them. She actually has them interacting,
making them healthy, because instead of sitting down watching TV, she doesn’t actually like TV…
Sit in one place and watch TV and pretty much now I’m giving any snack and they’re still sitting
watching TV. I don’t want that. I want them to walk around, I want them to get into an active
lifestyle. So instead… walking around and entertaining themselves by playing, constantly running
back and forth, running around - that’s why a lot of her floors are padded. And on top of that she
got the obstacle course. (27-year-old parent with 2 children in family child care)
9. Health insurance access
The early intervention providers who participated in the focus group identified that children
frequently lose their health insurance, and thought that this may be an area of intervention for child
care providers:
I was just thinking too when you said about insurance - but maybe letting the daycare centers
learn how to keep up on their clients’ Husky. Because they fall off. And then they don’t know how
to get back on. It takes me forever to get anybody back on… And daycare providers don’t know
that. People don’t know that… So give them a little bit of training on Husky.
10. Asthma
A health care provider felt strongly that asthma was an area where child care providers could be
educated to identify signs of escalation:
Like I said, with the asthma action plan, even if you’re talking about a daycare provider who
doesn’t really have any health background at all, if they are seeing a person who is in the yellow
zone all the time, and they are giving medication all the time, that needs to come back. They need
to say to the parent, “I need you to have this child go see their provider, because they’re just
wheezing too often. They shouldn’t be doing this.” They need to know that that’s not right, that’s
not normal. It’s not acceptable… These are more chronic problems, and the kind of things that do
require more serious attention. I think it’s certainly appropriate to try to help them identify a couple

Graber
63
of simple things that are like that. Asthma’s an easy one… I think asthma’s a great place to start,
because there are specific things you can do, there are specific things they are already called upon
to do. (59-year-old health care provider with 29 years of experience)
B. Training for family child care providers as health educators and advocates
Participants commonly believed that formal training and standardization of family child care
providers would make them better equipped to offer sound health advice and support to families.
Four main themes emerged in this discussion, including 1) general information training and
continuing education, 2) conversation and communication skills, 3) professionalization, and 4)
exclusion policies and standards.
1. General information training and continuing education
Many interview participants, particularly health care providers, expressed that they wanted child
care providers to know basic, correct health information so that child care providers could
appropriately share health messages with families. A community service provider said that their
training is critical, because they have such intimate access to families:
It’s all general information that they get as part of the training. Now, home childcare providers
will impart that information to parents, so that they can follow up at home. Because in doing so,
what they’re doing is educating the parent as well, informally. And they probably have a better
chance of getting the information across to parents than any professional would. (67-year-old
community service provider with 47 years of experience in New Haven)
A health care provider talked about standardizing the training and education that child care
providers receive in order to be licensed:
In licensed settings, I think if there was a way to provide more oversight, if there was a way to - I
hate to say standardize because we shouldn’t standardize. But if there was at least some things
that everybody - some bits of information that everybody has to know before they get their license,
some bits of information like continuing ed kinds of things that they were required to do to keep
their licenses, and a place where they can call if they have a question, that would be great. (51-
year-old health care provider with 23 years of experience)
Another health care provider agreed with the idea of basic training:

Graber
64
I think that they’re probably - to be a childcare provider they can be like - it’s important to be basic
life support, CPR trained for pediatrics, so they’ll have minimal information on that… Or maybe,
there could be like a training process for them. But if they’re going to be like a certified recognized
childcare provider… They have continuing childcare education that keeps them upto-date on the
latest childcare advice for basic care. (34-year-old health care provider with 1.5 years of
experience)
A community service provider agreed that training would be helpful for child care providers, but
was not confident that they would access these opportunities:
I don’t know whether there are certain like updates, or some kind of workshops they have to attend
like once a year just to get up to speed on this that and the other; whether they participate even if
it’s available… Even in [my] world, they offer so many workshops and trainings, but they’re not
mandatory, they’re just optional, and some people should be going to them, but they don’t! So I
don’t know. (62-year-old community service provider with 35 years of experience in New Haven)
Other health care providers were skeptical that family child care providers would be able to receive
the new standards or make the appropriate changes in their child care routines even if they did
receive the training. One health care provider expressed this concern, but then offers an alternative
focus for training:
Because I feel like what I could envision happening is some sort of guideline. But how many people
are really, especially the ones who are caring for those kids every single day, day in and day out -
when are they going to sit down and read guidelines like that. And, not only that, but they have
their ways that [they] think work. Just like I have my ways that I think work, about behavior
modification and parenting and everything else. And just because there’s a study to prove it or not
doesn’t make one opinion necessarily less… I think one thing that could be done is if you get wind
of some of those that could be potentially harmful, and sort of rumor-like, like the flu vaccine or
things like that, then you could focus provider education on those things. As opposed to giving
guidelines about what could be advised. I would say focus in on those things that may actually be
somewhat detrimental, to a community. (38-year-old health care provider with 7 years of
experience)
A health care provider also expressed skepticism, arguing that training child care providers is not
high on her list of community health priorities:
If we have a lot of money to spend on educating daycare people, then we might want to spend it
on some mental health coverage. There are probably online programs and daycare workers you
could throw together, and say, “Go online and learn this, and answer this questionnaire, mail it
in.” But -- or video courses or… I just think we have other things that really need one on one, and

Graber
65
that aren’t available. There are limited funds for stuff like that. In some ways, I guess you’re talking
about utopia. So in a utopia, I guess you would have classes for everyone who ever took care of
kids, including parents. (60-year-old health care provider with 32 years of experience)
2. Professionalization
Professionalization of family child care providers, meaning their continued education, training,
and formal collaboration with other family child care providers, health care providers, and
community service providers, may offer child care providers more esteem and stature in the
community. Creating a network of family child care providers additionally creates a professional
community, where individual child care providers do not have to feel so isolated. A few community
service providers called for the professionalization of family child care providers which, they
argued, would enable this organization, mutual support, and training. A community service
provider said:
But I think the more you can validate the important role that daycare providers have in the lives
of their families and they see that connection and you give them tools to make them feel more
confident, and you include them in a larger forum with people in similar roles and professions,
that you create this whole network. And similarly, it’s an opportunity for family daycare providers
to feel just [more] confident but that they have other peers that they can talk to. You bring them
into that role as being a very valuable community health advocate or health educator, for the
families, and you teach them how they can do that. You support how they can do it. (51-year-old
community service provider with 4 years of experience in New Haven)
A health care provider added to this argument, encouraging professionalism and training with
reflective supervision:
Because it’s certainly helpful to provide training to people and to provide educational
opportunities, and to make sure people meet credentialing standards, and that both fosters
professional pride in child care providers, and also enables them to get what they need, so that
they meet basic standards of care and surpass them, and they can check for themselves how they’re
doing. And all of that is really critical. And at the same time the professional support that goes
with the educational development and the capacity to have time for reflective supervision and also
meeting with other professionals, so that they’re not isolated in their homes, or for that matter in
their center, without a good support staff, where they really feel, and it gets back to our initial
statement about relationship building and trust, that they really can trust the person that’s
providing supervision to them who isn’t also their immediate supervisor, for example, so they can
really talk about their gut feeling and what they’re noticing and what their concerns are. And that,

Graber
66
I think, probably more than anything, is the most important part of the work. (45-yearold health
care provider with 16 years of experience)
3. Exclusion policies and standards
Health care providers felt that child care providers needed more explicit and informed policies of
exclusion to define explicitly when children cannot be cared for in child care, and in turn define
their role in the care of the child. For example, a health care provider said:
But I think it happens with the family childcare providers some too that deciding when do you send
the child to the doctor’s and when you don’t send them to the doctor’s. And I think sometimes some
of them are still, the child has certain symptoms, “I need a note from the doctor,” but they really
don’t need a note from the doctor. I think that’s a very hard area to decide how to help them. It’s
kind of a gray area, it’s a judgment call, and they’re much better if they can - they like the policy
to be: the child has this temperature, they need to go home. The child had a green runny nose for
this many days, they need to go home. So it’s harder when it gets into that gray area: well how’s
the child acting, do they need a lot of extra care. (61-yearold health care provider with 3 years of
experience)
A health care provider reflected on her frustration with child care exclusion policies:
Sometimes I see the frustration that parents have, and I do too, when daycare sends them home
for conjunctivitis, which I think is -- kid’s mom’s missing work. Conjunctivitis is not any more
contagious than a cold, but that frustrates you and I think-there’s really some -- I think, now you
bring up subjects like ringworm or conjunctivitis, things that they should not be missing school,
or daycare with the mom missing work, I find that a very frustrating thing and I wish there was
more of a blanket policy about what they should missing for, not just, “Oh, I think your kid has
conjunctivitis,” or they’re making mistaken diagnoses about “Your child should get checked up
for bronchitis” or something like that, and then the parents get all nervous about it, I think that’s
hard, then you have to backpedal, to kind of work a lot harder to say, “No, it’s not bronchitis.”
(35-year-old health care provider with 6 years of experience)
When parents were asked about exclusion policies, several expressed that their child care providers
were accommodating of their family’s needs, trying to care for the children until it affected the
care of other children under their care:
One day he was sick, this was like towards the end of the day so, and she wanted me to come get
him, and it was like 1 o’clock and I couldn’t get him until 3:30 or 4… And she’ll like bathe him,
just take care of him, put him in a different room, [away from the other] kids, but still check on
him. I felt like that was nice of her. She knew I couldn’t leave early, so she tried her best to keep
him calm… [My child care provider said that] she can’t keep watching him while he’s vomiting…
I didn’t want all the kids to catch it either, like if it was a virus. But she did handle it for a while.
(22-year-old parent with one child in family child care)

Graber
67
Another family, however, expressed frustration when their child care provider asked that they come
pick up their children for illness, as it implied that they were not being considerate of the other
children:
And with the sick, that my children are getting everybody else sick, that was just like, “Ok, these
are babies. And I’m not bringing my children to daycare with the plague.” I thought that was
rude… They’re children. They carry germs. They’re playing. They’re putting stuff in their mouth.
They’re hugging. They’re sharing popsicles. (27-year-old parent with 2 children in family child
care)
C. Modeling healthy living and facilitating change for families at home
When child care providers incorporate healthy nutrition, hygiene, and behavior management into
their child care, the interview participants reflected that families can learn from these examples
and can facilitate changes in their own homes. Parents, health care providers, and community
service providers identified 1) behavior management and development, 2) nutrition, and 3) oral
health as areas where child care providers could show families how to live healthfully at home.
1. Behavior management and development
Parents, health care providers, and community service providers agreed that child care providers
could model appropriate development and behavior management for families. For example, a
parent said that she learned how to discipline her child from observing what her child care provider
did, which empowered her to ignore the expectations of her community:
[My child care provider] told me certain things to do, like I don’t usually discipline him, but she
was like, “you know, just put him in time out, you know the time out chair, you know he has to
learn he can’t talk back to you or he can’t do certain things, you have to stick up for yourself,
because he has like anger issues.” So she was like, “you don’t have to pop him or anything, just
tell him, [child], you’re going to go on the time out thinking chair.” So he knows the thinking chair
is like the time out chair. She just taught me a lot of ways to handle him. Other people around me
like, “you should beat him,” and I tell him that he’s not using his “listening ears;” [my child care
provider] calls it the “listening ears.” So he has to put on those to listen and, you know, behave.
She taught me a lot of stuff on him. (22-year-old parent with one child in family child care)

Graber
68
A health care provider agreed that child care providers can model healthy developmental stages
and behavior, saying:
I think that’s one way that childcare providers can work with families, if they model different
things, for example, [one child’s] mom would always send him with a bottle to [child care], but
[the child care provider] immediately didn’t use it, she sent it back home, I believe she sent it back
home with the juice in it. So I think that’s one of the areas they can do work with, in modeling. I
think how they handle the child, behavior-wise, is another area that they could possibly be very
helpful with, if they’ve found a way to work with that child, I think that’s another way that a parent
can kind of observe. (61-year-old health care provider with 3 years of experience)
A community service provider explained how child care providers can educate families about
disciplinary techniques by explaining the “rules” of the child care to them:
The daycare provider can say, “Here we use timeout when the child does something appropriate,
but we don’t park them in the corner for 15 minutes, we just remove them from the activity where
the problem is, and they are there watching everybody else having fun, but they have to be there
for one minute or two minutes, because it’s one minute per age, and then they can come back.
That’s how we’re going to deal with discipline here.” They can also talk about, “We also use other
type of strategies, like children have to learn how to wait. You tell them that first they have to clean
up their dish or throw their trash away and then they can go back to playing.” (62-yearold
community service provider with 35 years of experience in New Haven)
One parent recalled that she learned to child proof her home from her child care provider:
[My child care provider] showed me a few things about… a healthy environment for a child. Plus
she has also gave me some, like the plugs to stick in [electrical outlets]… And she gave me the
thing that you lock the cabinets up with. That’s what I did. I had to childproof my place a little bit
for my son. She had told me about childproof, making sure I childproof. (41-year-old parent with
one child in family child care)
A couple of parents said that their child care providers initiated their children in toilet training. For
example, another parent said:
She’s been dynamic in his potty training at this point. Very. Very. I have to give her credit - she
started it. And he’s done very well, celebrating a first week of overnights with no diapers, no
messes, and good mornings. (41-year-old parent with one child in family child care)
2. Nutrition and healthy eating
Health care providers, parents and community service providers also all agreed that nutrition and
obesity were areas where modeling by family child care providers may be beneficial. For example,

Graber
69
a health care provider reflected upon how children can be introduced to healthy foods at child care
that they otherwise would not receive at home:
One of the things that you always have to ask is, when we’re worried about the kid’s weight either
because it’s too much or too little, “Do you send the food to the babysitter or does the babysitter
cook?”… [and the parent replies] “Well, but he does get [vegetables] at the babysitter’s because
the babysitter makes stuff that I don’t eat.” Or “Why will he eat this at the babysitter, and when I
make the same thing at home, he won’t eat it at home?” (51-year-old health care provider with 23
years of experience)
One parent said that after trying foods at child care, her child was interested in eating healthier
foods at home:
[My child care provider] makes sure everything is laid out to keep a child safe and healthy, for a
healthy environment. And far as the certain food she gives him, the healthy food… She was feeding
him yogurt. When I came to pick him up -- actually I got yogurt in the house -- he opened the
refrigerator and get it himself so I know that’s what he want. (41-year-old parent with one child in
family child care)
A parent says that her child care provider teaches her how to make healthy foods that are still
appealing to her child:
[My child care provider] always let me know what he eats every day. And she tells me different
things on how she makes him eat it, like she’ll add a little bit of garlic, so I can make it at home.
(22-year-old parent with one child in family child care)
3. Oral Health
Parents and health care providers expressed appreciation when child care providers encouraged
children to brush their teeth during the day. For example, a parent learned about when to start oral
health care from her child care provider:
I didn’t know that he was supposed to go [to the dentist] -- I thought they wait -- because he’s my
first child, so I thought they wait til they’re about 5 or 6, and since he was a baby, [my child care
provider was] like, “start brushing his gums.” But I never knew that and I wasn’t listening at first,
and then she was, “he has a mouthful of teeth and you have to start brushing them.” But she
started brushing them at school… and then I started brushing them at home. And now he knows
how to brush his teeth. (22-year-old parent with one child in family child care)
A health care provider agreed:

Graber
70
I think… around oral health today, if the parent know that the provider’s brushing the teeth at the
family childcare home, then I think that places an additional emphasis and I think that’s good
modeling. (61-year-old health care provider with 3 years of experience)
D. Shared and repeated messaging
Interview participants reflected on how families positively responded both when they heard the
same health message from different people (“shared messaging”) and when they heard the same
health message multiple times (“repeated messaging”). Three prominent themes emerged from the
interviews, including 1) the role of shared and repeated messaging in helping parents understand
health education, 2) identifying others to reinforce messages, and 3) standardizing health
messages.
1. The role of shared and repeated messaging in helping parents understand health education
Parents and community service providers found families more open to health education and
messages when they were shared between different, reinforcing individuals, and when they heard
the message multiple times. For example, one parent said:
Because at one point, [my daughter] was talking a lot sooner than [my son]. So I would talk to
[my child care provider] about it, and she was like, “No, he is trying to talk,” and then we
compared it with the notes from our doctor, and the doctor was like, it’s the same thing, “Boys
kind of speak a little later.” It’s usually between them two, and we figure out what we’re going to
do, or whatever the answer might be we go from there. (31-year-old parent with one child in family
child care)
A parent felt comforted when her child care provider and mother were saying the same things about
her child:
I take what [my child care provider] says, I take that there to heart, and also, my mother, she be
like, “I told you that girl need to be doing [these exercises], you need to lay off this,” and I’m like,
ok, I’m hearing this from two people now. (38-year-old parent with one child in family child care)
A parent shared that she initially felt defensive when her child care provider expressed concern for
her son, but then after hearing many people express this concern, she sought help:
My initial [reaction] was like, “He’s perfect, he’s fine, what is she talking about?” Like I said,
once I got past that and several people were saying to me, “No, there is… his eye does look

Graber
71
smaller,” then I was like, ok. Enough people are saying something about it that I have to, I would
be wrong if I didn’t check into it at this point. But initially it wasn’t that easy, taking that, hearing
that. (41-year-old parent with one child in family child care)
2. Identifying others to reinforce messages
Health care providers expressed that they like to connect families with services and organizations
that will repeat their health messages. Social service providers, however, look for other authority
figures to authenticate their health messages. For example, one health care provider said that she
often branches out to connect families with other agencies for this purpose:
The other thing that I tend to do is I tend to branch out. So if they’re younger and under 5,
especially with obesity or failure to thrive-related issues, I will call WIC and I’ll have WIC
reinforcing what I say. And I communicate directly with them… And the behavior stuff, it’s harder,
if there’s school-based health then I’ll talk to the schools, I’ll talk to the social workers and the
counselors there, I’ll do what I can. Because I know that I as a single person am likely to not be
fully effective. (37-year-old health care provider with 7 years of experience)
A community service provider said that she depends on WIC and health care providers to reiterate
messages about healthy eating:
If it’s something that has to do with food and eating, we always encourage to either talk to the
WIC provider or their [health care] provider, just so that there’s more people repeating the same
message. (51-year-old community service provider with 5 years of experience in New Haven)
A health care provider recalled a time where she struggled to help a family decide on a treatment
plan, so she reached out to their pastor for assistance:
I said [to the family], “What is getting in the way of your understanding or feeling comfortable
following what I’m telling you?” And she said, “God will cure this.” And I said, “Well who do
you work with to help you with that?” And she said, “Our pastor.” And I said, “Do I have your
permission to call your pastor?” And she said, “Yes.” And I did. And I talked to Pastor so-andso.
You have to figure out what your obstacles are. (60-year-old health care provider with 32 years of
experience)
An early intervention provider said that child care providers often turn to her to substantiate the
health messages that they are giving parents:
I think the advice that I’ve heard a lot of daycare providers, and I think it falls under health, is
around sleeping and eating issues and nap issues. And some of the advice is appropriate, “You’ve

Graber
72
got to get your child off the bottle,” and some is not appropriate, depending on the quality of the
provider. And sometimes what I get a lot is daycare providers complaining to me about a parent
not doing xyz, “She has to get rid of that binky, that mom, I keep telling her to get rid of that
binky,” and then kind of looking to me to be the one to reinforce [that] what the daycare providers
typically are recommending [is] the correct course of action.
Another early intervention provider agreed, saying:
I think before they speak to the parent, they look to us for validation. If they have suspicion about
a child, and it’s almost as if they ask the [early intervention] provider first, “What are your
thoughts, because we’re thinking of talking to the parents about this.” But it does come along
with trust [between the early intervention provider and the child care provider].
A community service provider commented on how recognizing her own role as a home visitor
enabled her to collaborate with health care providers more effectively:
Because I can’t diagnose, and I can’t change medication, but I can certainly talk about what we
saw when we were in the house, by working with the kid, but then to bring it back to the doctor
that says, this is it, this isn’t black/white, what do you think? Maybe it should be done differently.
(52-year-old community service provider with 28 years of experience in New Haven)
However, as described by this early intervention provider, any multi-disciplinary collaboration
needs to be performed carefully; here she describes a situation where collaboration between the
child care provider and the health care provider led to the parents to withdraw from care:
I did have one daycare provider that did speak to a doctor regarding the parent’s choices of food.
And the parent became very upset and pulled their child from the daycare. So you can see what
happens. Now the parent did give the daycare a release, but I guess the doctor also agreed with
the daycare provider, and the doctor called the parent directly, saying that the daycare provider
had said this.
Thinking more broadly, one community service provider stated that too much “siloing” can reduce
our ability to collaborate and meet families’ needs:
Sometimes the lines we draw as professionals kind of keep us in business, so to speak, as opposed
to breaking down the barriers to actually having the person get help. (52-year-old community
service provider with 18 years of experience in New Haven)

Graber
73
3. Standardizing health messages
Community service providers and health care providers expressed that they wanted a standardized
set of health messages for child care providers to share with families. A community service
provider said that she believed shared messaging was important because families are otherwise
overwhelmed with the different health messages that they receive:
I think what we’ve observed is they just stop [when they hear different health messages]… they
stop critically thinking about it, get stuck, and don’t act one way or the other, or they feel uncertain.
(51-year-old community service provider with 5 years of experience in New Haven)
A community service provider said that she believed that sharing consistent messages would be
less confusing for families:
To be consistent in the message, to connect them with things that are available in the community…
And again, you’re reiterating, and just saying, “Like we said before, this is this and…” Because
folks are confused already about how to navigate the services that we say are available to them.
(46-year-old community service provider with 15 years of experience in New Haven)
Several participants said that if child care providers were sharing standardized messages with
families, they would feel more comfortable with them as health educators. For example, a
community service provider said that she would have more confidence in child care providers
giving health education if she knew where their information came from:
I think it’s great that there’s a concern and that information is being offered up, but how do we
determine if it’s the right information? If it was something that the American Childhood Provider
Council, [or] whatever, said that “Ok, everyone who’s doing this work needs to attend this type of
training,” then it’s all the same information… but again, if there’s some kind of like certification
on the wall of our center saying that all of our staff has gone through this federal something or
other, so that means we’re all giving the same information. (46-year-old community service
provider with 15 years of experience in New Haven)
A health care provider agreed, believing that shared messaging would add accuracy to child care
providers’ health education:
And who are those people, and shouldn’t we make sure that those people are all giving the same
information? Because some people give pretty screwy information, that’s several iterations old.
(51-year-old health care provider with 23 years of experience)

Graber
74
E. Role definition and knowing personal limits
When thinking about child care providers sharing health advice, health care providers and
community service providers expressed concern that child care providers would potentially act
outside of their role or expertise. Several participants thought it was important for child care
providers to define their specific role, specifically distinct from health care providers. For example,
one health care provider said:
I think one thing that I would say is that I feel like parents sometimes come in with a diagnosis.
They’ll say, “She has the flu.” Or he has this or he has that… I think helpful hints is one thing, but
actually taking on that role as the medical provider oversteps their boundaries… Actually trying
to participate in the medical care of a child is something completely different, and probably best
left to others. (38-year-old health care provider with 7 years of experience)
A community service provider encouraged people training to be licensed family child care
providers that they must recognize their professional role and how it is different from their being
a knowledgeable community member and a health care provider:
Look, these are things that you need to be doing with the parents: informing them, giving them
information. But you cannot make tea, make a special tea. I know that in our community, whenever
we got sick, we would always have our special tea. Well, remember, you’re now a licensed home
childcare provider, you’re licensed by the state, you have to follow the legal parameters. You’re
now a professional. You have to watch out for your business because you are now a licensed home
childcare provider, and this is your business and you don’t want a parent suing you because of
something that you gave their child and you gave to them to give to their child. You’re not a doctor.
You’re not a pediatrician. (67-year-old community service provider with 47 years of experience
in New Haven)
This role definition may be especially important for vulnerable families. One health care provider
said that child care providers not only must be thoughtful about their role as health educators, but
also about the families receiving this advice:
I think they shouldn’t be handing out medical advice in the same way that your grandmother
shouldn’t be handing out medical advice and saying that it’s fact. If you say, “This is what I think.
Maybe you should go check that out with your pediatrician,” that’s one thing. But saying it as if
you’re the substitute in most situations, the substitute for the pediatrician, probably isn’t - I’m not

Graber
75
so fond of that. … But I think there’s a line, and lots of people cross lots of lines, but it depends
on - you cross a line and you’re giving information to somebody who doesn’t know any better,
somebody who doesn’t know to question the information, that’s not good, in my humble opinion.
You cross a line and you give somebody some information and that person says, “Ok, I’ll think
about that, and I’ll ask somebody who I think has more background in this area than you have,”
that’s fine. (51-year-old health care provider with 23 years of experience)
Further, a health care provider, when challenged by a child care provider, wanted to remind her of
her responsibilities:
I just saw a kid this morning [in the clinic] where the teacher said [to the parent], “Take him back
to his doctor and tell the doctor to do something…” My initial response was to push back: I’ll
send her a note saying, “teach this kid to read!” [laughs] “You do your job!” But again, so we all
have that, everyone has that sense of defensiveness. (61-year-old health care provider with 31
years of experience)
Defining roles and limits of a position, a community service provider said, helps alleviate burden
from a home visitor:
It might be because I so strongly believe in [collaborating with health care providers]. It also takes
the burden off the home visitor, and I feel like that’s really critical to help them understand what
their limits are, and to remind them consistently of what their limits are. So their focus is on early
childhood development and supporting the mom with engagement, [we have] other people that
can help with this [health concern]. (51-year-old community service provider with 5 years of
experience in New Haven)
VII. An example: Issues of child development and potential developmental
delay
Communication with parents around the diagnosis of developmental delay is difficult in the best
of circumstances. For children living in poverty with suboptimal access to health care and parents
and child care providers with limited formal education, communication around the diagnosis can
be overwhelming.
In this study, parents, health care providers and community service providers revealed four
recurrent themes around the discussion of developmental delay which integrates many of the

Graber
76
themes identified previously in this study, including 1) parents who are overwhelmed by poverty
and are then told that their child has deficits experience denial, guilt, and anger, 2) concerns about
development may hold a particular space in parents' sense of guilt because of the perception that
the parent may have prevented it, 3) health care providers' should balance their expertise with their
limited experience with the child, and 4) family child care providers' should balance their
experience with the child with their limited expertise.
A. Parents experience denial, guilt and anger when told that a child has
developmental delay
When sharing that a child has developmental delay, participants felt that parents responded with
denial, guilt and anger, further exacerbated by poverty and a myriad of life stressors. A parent
reflected on why child development is such a personal and sensitive issue:
You’re dealing with their children. You’re dealing with something that’s closest to their heart. And
anything you say or do have a direct effect on their heart. So your commentation [sic] should be
more perceptive because of the fact that you’re dealing with a sensitive issue. Like no one wants
to hear that their child is this or that or something’s wrong. No one wants to hear that. But even
truly if it does exist, no one wants to hear it. (27-year-old parent with 2 children in family child
care)
A community service provider echoed this sentiment and the gravity of learning your child has
developmental concerns, calling it the “death of a dream:”
Every family has a dream. Their dream is they’re going to have a family and it’s going to look like
“this.” And they’re pregnant and they envision what their kid is going to be like. And then the kid
is born, and the kid is who they are. And the kid might have autism or selective mutism or a variety
of other developmental delays of some kind. And I always say, it’s the death of the dream. That
happens, and then parents go through a process of huge amounts of denial, a lot of resistance
about labeling, and a lot of confusion, and a lot of - they’re very disoriented, because they’ve lived
their whole life with this dream, whether it was conscious or not. All of us have this dream… Those
things are just as much an issue of special attention needs, as a kid with a diagnosis. In some ways
a diagnosis is easier, because it’s like, ok, your kid is blind. This is what we do for kids who are
blind. You know? But the other things are more elusive. (63-year-old community service provider
with 18 years of experience in New Haven)

Graber
77
A health care provider said that discussing concerns of developmental delay can be interpreted by
parents as an insult to their understanding and familiarity of their child:
The parent doesn’t want to be challenged in their capacity as a parent-- to be the first person to
understand that there might be something concerning about their child, and as a parent they have
that desire to be the person who knows everything, holds all of that information and that concern
themselves, is I think the primary issue. Along with, right up there, “There’s nothing wrong with
my child. You’re causing it.” There are so many concerns for parents in that setting. (45-year-old
health care provider with 16 years of experience)
Further, a health care provider reflected on her experience working with parents of children with
developmental delay or behavior problems:
I think people get very defensive thinking that their child may have some behavioral problem. I
think that’s a really difficult thing. People have children that may be autistic or behavioral issues;
I think it’s really hard-it’s easier to say my child has asthma than to say my child has autism. It’s
a really hard concept for people to accept, if their child has some kind of developmental problem.
It’s really difficult, and I can see why. So I think a lot of it is denial unfortunately. (35-year-old
health care provider with 6 years of experience)
B. Perception that parents could have prevented a developmental delay
Parents, health care providers and community service providers reflected that some responsibility
is placed on parents for their child’s development and behavior. Even while acknowledging
external stressors, a health care provider perceived that a child’s behavior is related to the “way
that they are being dealt with by their parents:”
And part of the problem is, with a behavior problem in particular, it’s not - sometimes it’s just built
into the kid. But more often it’s the way that they are being dealt with by - I hate the word
“parented,” but the way that they are being dealt with by their parents, and the way that their
parents were dealt with when they were young, it’s what they’re used to. If the only thing that
happens in your house is screaming, you were like that when you were a kid. You just don’t
remember. And it is hard… They really have to be in the right frame of mind and not thinking about
how they’re going to pay their rent or where they’re going to get their next meal, or where they’re
going to get clothes, and stuff like that. (51-year-old health care provider with 23 years of
experience)

Graber
78
When parents feel guilty because of the perception that they may have been able to prevent their
child’s developmental delay, they may become defensive. A 61-year-old health care provider with
3 years of experience in New Haven described this perception:
I think parents become more defensive in general… I think they take it more as an affront, that
you’re saying they’re not taking good care of their child, more than the physical [concerns].
(61year-old health care provider with 3 years of experience)
Parental defensiveness may lead to the child not getting needed services. A health care provider
recalled a story about a parent canceling early intervention services, because her role as parent was
insulted:
And then the family, there were psychological issues for the mom around some of the in-home
services in place. It made her feel bad, it made her feel bad as a parent, so she stopped it… And I
will just say, the combination of having the developmental disability, developmental and
behavioral disability, and being an underserved kid is a very toxic combination. Because this stuff
happens. Parents don’t know how to be good advocates. (50-year-old health care provider with 21
years of experience in New Haven)
A solution offered by one participant is to acknowledge the difficulty of the process for the parent
and emphasize parental self-efficacy in the process. A community service provider said that she
purposely turns to the parent as the individual who can influence the child’s development in the
future:
I always say to them, “There’s always programs out there, that can help you, you, not the child,
you - that can help you how to work with your child.” Because once you put the emphasis on them
and not on the kid - so you always say, “We’re gonna help you, as a mom, how to deal with
whatever situation that your child might have. It’s work that we’re gonna do with you that is gonna
help you through all his life, not [only] now.” (66-year-old community service provider with 40
years of experience in New Haven)
C. Health care providers' have expertise but limited experience with the child
Health care providers perceived that they have the expertise and tools to diagnose developmental
problems. They also argued that the perspective of the child care providers was based not on
standardized assessments but on a child’s role within a group of children. Parents, on the other

Graber
79
hand, wondered if the limited time the health care provider spent with the child would limit their
ability to properly diagnose a developmental problem.
One health care provider referred to the standardized screeners used in pediatric health to more
objectively determine a child’s developmental stage:
Pediatricians need to use to standardized screening measures, period. Because their eyeballs and
their time, their training, all of it, is not sufficient to know [if a child has developmental delay].
The kid who’s not sitting at 12 months, you don’t even need to be a doctor to know that that’s not
typical. It’s the kids with the more subtle findings, that’s the kids that you’re sort of often not so
sure about and you have to use standardized measures. (50-year-old health care provider with 21
years of experience)
Health care providers shared that they felt that as child care providers cared for multiple children,
their understanding of a child’s development may be skewed. A health care provider said that he
must assess the validity of a child care provider’s concerns about development:
[The parent and I will] talk about [their child’s development]… just to get a sense, is this real,
because sometimes people are being referred when it doesn’t really sound like they ought to be, a
teacher that’s just overloaded, and the mother doesn’t think the kid’s got any problems, so right off
the bat, you know that that’s not necessarily the problem that the teacher may think it is. (59-year-
old health care provider with 29 years of experience)
A health care provider reflected on how he has unique insight into a child’s development as he sees
them as an individual, and not as a part of a group:
I think the dynamic tension between the child care provider and the pediatrician is that they’re
looking at this child in a group of children, and I’m looking at one-on-one. And that I may have
an ability to have the child talk to me or to interact with me, whereas he may be totally different
in a group setting. (61-year-old health care provider with 31 years of experience)
Parents, in turn, expressed a desire that their health care provider had more experience and time
with the child. One parent said:
As far as our doctors are concerned, I understand there’s a lot of kids and it’s a multi-doctor
practice. Sometimes I do wish there was a little more time with the doctor. It always seems like it’s
in and out, fast. I wish we had a little more time to sit down and talk with them. But it is what it is

Graber
80
with the whole medical thing, how everybody’s trying to squeeze in as many appointments as they
can. Which kind of sucks. That’s the one thing: I wish we did have more time with our individual
doctor. (31-year-old parent with 2 children in family child care)
Reflecting this same concern, one health care provider expressed frustration that she cannot
connect families with the developmental services that they need because of time limitations and
lack of services in her clinic:
But how do you convince a family otherwise, in the short period of time that you have? At the
school it was a lot easier because I had more time, I could sit down with the family, I saw them
every day if I had to. But here it’s different. You’ve got 15-minute slot… Sometimes I’ll call and
I’ll be like, “Look, please, please, please, I’m begging you, this family, blah blah blah. Can you
help me out, can you get them in, can you…” and if I need some extra attention at a school that
we don’t have a school-based health center, I’ll be like, “Please, just check in, just let me know
how they’re doing, see if they need anything,” that kind of thing. (37-year-old health care provider
with 8 years of experience)
D. Family child care providers have experience, but limited expertise
In comparison to health care providers, participants expressed that family child care providers have
experience and intimate knowledge of children, but lack specific expertise in child development.
A health care provider acknowledged the experience of family child care providers, but expressed
that they lack the broad, objective understanding of a child’s individual development:
I feel like childcare providers in general have a good sense of, if they’ve been doing it for a long
time, of what a person that age should be doing. But of course they always have to keep in mind
that there’s a range as well. For example, if they’re going to an English-speaking daycare, but
they speak Spanish at home, they might have some differences in their language skills because
they can’t communicate in one language, they can communicate in another language… So in those
cases you have to rely on the parents’ report too. And parents’ concerns are usually really accurate.
So you have to take what other [child care] providers say with a grain of salt as well, and [do]…
as objective an assessment as you can do. (34-year-old health care provider with 1.5 years of
experience)
Another health care provider acknowledged the specific experience of child care providers and
postulated how their insight may be helpful in diagnosing children:
I think if a daycare provider’s had a lot of experience and they have a kid who has unusual
behavior, just like a school teacher, I think they are a valuable link. There’s no question they see

Graber
81
more than I do. I have the kid in here 30 minutes. So I would say, yeah they should do that. I think
that they just need to educate themselves. (60-year-old health care provider with 32 years of
experience)
A parent, whose child care provider expressed concern about his child’s development, agreed that
child care providers may understand the context in which they are working but did not have a
“professional” reason to make the assumption:
This wasn’t discussed between you, or between us, like you just come out and just say, “What do
you base that on?” and she couldn’t even tell us like he’s not as fast as other kids in the class…
But you telling me you basing this by the kids that in his class, and he’s the only male in his class.
So that’s not a actual professional assumption [sic]. (27-year-old parent with 2 children in family
child care)
A community service provider reflected this same view, that child care providers have experience,
but lack the larger context and framework to balance their observations:
I think that childcare providers, both center-based and family childcare, need to know what’s age-
appropriate. It gets very easy for providers or teachers to say, “There’s something wrong with this
kid,” rather than to say, “You know what? Kids hit each other when they’re 18 months old, and
they’re gonna hit each other, and we’re going to do our very best to keep that from happening, but
it is gonna happen, and there’s nothing wrong with that kid.” To really understand when the kid is
over the line and when the kid is not. (63-year-old community service provider with 18 years of
experience in New Haven)

Graber
82
DISCUSSION
This study adds to the literature on the role of family child care providers as health educators and
advocates. Parents, community service providers, and some health care providers see a role for
family child care providers in providing health education to families, and differ in opinion about
what this role should be.
Hierarchy of need for vulnerable
families
Several interview participants alluded to the
challenges that vulnerable families face that
often take precedence over the health of the
family. Acknowledging that
vulnerable
families are often struggling with basic needs,
interview participants expressed
understanding that discussions around health and development were overwhelming, and often
received with compounded denial, guilt, and frustration. Abraham Maslow’s A Theory of Human
Motivation outlines a hierarchy of needs for individuals (Figure 3), whereby they are not able to
think about their safety (i.e. their personal security, protection, financial security, employment,
health and well being) without first meeting their physiological needs, including food, shelter and
clothing. While Maslow uses this theory to explore identity, personality and self-esteem, from the
perspective of vulnerable families, we think more about the base of the pyramid. For children (73)
and vulnerable populations (74) , this model reminds us that before changes in behavior and health
education, families must deal with their basic needs. As Maslow writes:
Figure 3. Maslow’s Hierarchy of Needs
Self
actualization
Self
esteem
Belonging &
Love
Safety
Physiological

Graber
83
If all other needs are unsatisfied, and the organism is then dominated by the
physiological needs, all other needs may become simply non-existent or be pushed
into the background. It is then fair to characterise the whole organism by saying
simply that it is hungry, for consciousness is almost completely preempted by
hunger. (75)
In this hierarchy, employment and income are crucial in enabling families to move past their
physiologic needs. Child care is inextricably linked to a family’s employment; we argue that child
care is a basic necessity that families must obtain before they can begin to consider their health
needs. The importance and burden of child care is further emphasized by the amount of money
families dedicate to child care. The Connecticut Voices for Children reported that families of four
with a yearly income of $55,440 spend 27% of their income on child care, more than housing
(21.3%), food (13.4%) and health care (8.1%) (76) .
As child care providers are taking care of children and helping parents with one of their basic
needs, they can potentially play a part in helping families move up Maslow’s pyramid. If a family
child care is an emotionally safe space, where parents have confidence in the care their child
receives, child care providers can provide support to parents so that they can begin to contemplate
their higher level needs. The community service provider who offered a parent support after
expressing concern about a developmental delay provided assurance that she would help the parent
so that the family was not facing this concern alone.
Trust emerges from good communication and relationships
Between parents and child care providers, health care providers and community service providers,
and child care providers and health care providers, personal relationships and communication
beget trust and collaboration. Data from this study demonstrates that parents appreciate hearing
from their child care provider regularly as it affirms that the child care provider cares for the child

Graber
84
and knows the child’s needs intimately. Over time, seeing a child care provider continuously care
for a child potentially builds a long-term relationship between the family and child care provider
and in turn has the possibility to increase information sharing, especially in areas of health and
child development. One can extrapolate that this relationship and frequent communication may lay
the groundwork for more challenging conversations, including a child care provider expressing
concern for a child. On the other hand, these data demonstrate that child care providers would
likely benefit from training around how to communicate with families, especially when expressing
a concern. For example, when discussing developmental concerns, child care providers could
anticipate that communicating with families will be challenging and possibly controversial. They
should be encouraged to set aside specific time for this conversation and to create a plan of how
they want to share the concern with the family and then offer support and resources for assistance.
This study demonstrates not only that parents depend on a myriad of different people in different
roles for their health advice, but that child care providers and community service providers can
identify and collaborate with a parent’s health care provider in order to more comprehensively care
for a family. As many parents expressed, child care providers are accessible, experienced, and
share messages about parenting, health, and development. Without personal relationships between
child care providers and health care providers, however, this collaboration is limited. While health
care providers and community service providers reflected that their mutual relationships allowed
them to better access families in need, child care providers were rarely mentioned as part of the
cadre that cares for young children as depicted in Crowley’s Ecological Model (53). If child care
providers were able to foster relationships with health care providers, collaboration would be more
conceivable. This process, however, would be overwhelming for both child care providers and

Graber
85
health care providers given the number of children and number of child care providers. Instead,
institutional relationships, as suggested by an interview participant, may be more realistic for
collaboration. One option is to consider the model of the family child care provider networks.
These networks or organizations may be able to help connect family child care providers to health
clinics or clinic representatives to initiate more open communication, support, and training around
health messages and concerns about individual children. As HIPAA and confidentiality must also
be navigated, a centralized child care provider network may be able to provide support in assisting
individual family child care providers to obtain consent from their parents. In order for such
collaboration to work, however, child care providers, organizations, and health care providers need
to be explicit in defining their individual roles, so as to decrease confusion for families. It is integral
that each party understand the limitations of both their position and their knowledge base and that
of the other involved individuals. With this acknowledgment, all collaborating partners can then
dialogue about the concerns of a family and ideally recognize the insights of each member.
Extension of the Medical Home: A case for collaboration
As Bronfenbrenner’s and Crowley’s models address, there are several individuals (and larger
systems) invested in a child’s health. The medical home, also situated within the social ecological
framework, benefits more from the connections between health care providers, community service
providers, child care providers, and families. This is reflected in three areas: 1) the existing
collaboration with schools in school-based clinics, 2) medical home outcome measures are found
in family child care, and 3) collaboration with child care providers potentially mediates both the
need to additional care coordination and the tension between experience and expertise.

Graber
86
Existing collaboration with schools in school-based clinic: reaching children
“where they are”
The concept of a medical home has broadened the definition of caregiver, recognizing not only the
pediatric provider, but also the number of other caregivers in a child’s life, from subspecialists, to
school providers, to child guidance clinics (13, 14). As the most recent AAP policy on the medical
home recommends that providers have “Interaction with early intervention programs, schools,
early childhood education and child care programs, and other public and private community
agencies to be certain that the special needs of the child and family are addressed” (14). Schools,
via school-based health centers and school nurses, have worked to extend the medical home model
into a place consistently frequented by children and families, meeting families in places where
they have other reasons to go. The AAP Council on School Health identifies the school nurse as a
“medical home extender” (77) . Lindlay et al write that while they do not assume that the school
will be able to act as a full medical home, they believe that their regular access to children may be
able to provide needed supplementary care, including access to vaccines (78) and health education
about obesity, pregnancy, sexually transmitted infections, drug and alcohol abuse, and violence
(79) . The increasing evidence of the role of the school-based health center to act as medical home
extender and medical home partner for school aged children, has not been matched by a
corresponding assessment of the potential for child care programs, or child care providers, to act
in this role for pre-school aged children. Child care programs are places that similarly have regular
access to children and therefore may offer some of the same benefits in partnering and extending
the medical home. Given the increasing evidence on the importance of the first five years of life
regarding brain growth (80) , and the interventions that can improve outcomes (46) connecting the
medical home to child care programs and child care providers becomes increasingly important.

Graber
87
Medical home outcome measures are found in family child care
In this study, parents interviewed described their child care providers as “family centered” and
“trusting,” two of the outcomes consistently measured in studies on the effectiveness of medical
homes (19, 25-27). As parents and community service providers discussed, personal relationships
with child care providers, open communication, and a sense that child care providers understood
the situation of individual families created a trusting relationship. Interviews with parents in this
study reflected that the absence of one of these elements led to frustration and lack of trust.
Similarly, as found in Rosenthal’s previous research, family child care providers who have a strong
relationships with families are able to provide more health information: “when the relationship is
described as collaborative, [child care] providers feel empowered to provide extensive health
promotion” (29). The qualities of personal relationship, trust, and patient-centeredness are
reflected in the medical home literature, where these same qualities were found to be associated
with a greater likelihood of behavior change and increased access to health information (19, 25-
27). Collaboration between child care providers and health care providers could extend this trust
and family-centeredness to the child care home, and potentially allow for shared messaging and
facilitation of health changes at home.
Benefits of collaboration with child care providers
Health care providers in this study discussed the difficulty they have in achieving the advocacy
and care coordination that many families need, including connecting them with various social
services and neighborhood programs, enlisting additional support from schools, and navigating the
hierarchy of needs of a family. As child care providers are often grounded in the same community
as the families with whom they work, child care providers potentially could assist in connecting
families with the services that they need and support them in reaching out to these services. As a
community service provider said in an interview, child care providers “probably have a better

Graber
88
chance of getting the information across to parents than any professional would.” Appropriately
defining their role is critical, however, as they must learn to enlist the most qualified support for
families and not necessarily assume this role themselves.
Further, interview participants identified the tension between child care providers and health care
providers and between experience and expertise. Both perspectives are needed in the care of a
child and both perspectives are valued by families. Collaboration between child care providers and
health care providers potentially would diffuse this tension and, in turn, would allow for
information sharing, shared messaging, and a more comprehensive approach to the family. The
extent and intimacy of the collaboration, however, needs to be characterized specifically with the
family. As some families were unsure about the collaboration between health care providers and
child care providers, one family articulating that not all health information should be shared and
another firing a child care provider for talking with the family’s health care provider, this
relationship needs to be approached with great sensitivity. As both the child care provider and
health care provider are working in the best interest of the child and family, the family’s comfort
with information sharing between the health care provider and the child care provider must first
be assessed, and then revisited professionally throughout their working relationship. For some
families, more general collaboration between health care providers and child care providers, such
as shared messages about healthy nutrition and developmental milestones, may be more beneficial
than personalized health education.
Scope of health advice from family child care providers
Health care providers, parents and community service providers agreed that the scope of advice
from child care providers to families should be limited to agreed upon topics. Interestingly, the
topics that participants from this study felt were appropriate for child care providers to discuss

Graber
89
were the same as were indentified in Rosenthal’s previous research, including nutrition,
development, and medication administration (29, 30). As our study’s interviews also suggest,
Rosenthal discussed the possibility that “The scope of this role [of the family child care provider
as health educator] was defined by the nature of the parent–child care provider relationship” (29)
. It is possible that the scope of health topics would be different for each child care provider,
recognizing their own limitations, their relationships with families, and their sources of support
and knowledge. While some topics, such as diabetes or broken bones, more clearly fall into the
expertise of health care providers, other topics, including nutrition, normal child development and
discipline are areas where experience with children may be most beneficial when working
and communicating with families. Figure 4 attempts to simplify and distribute some of these topics
on a continuum between expertise and experience in a theoretical model. On the left hand side of
the model are health topics that require more expertise, meaning medical knowledge and training,
and include, for example, the appropriate use of antibiotics. On the right hand side are topics that
Figure 4. Scope of f
amily child care provider health advice
More
%
Exper)se%
More%
Experience%
D %
Pneumonia%
Asthma%
Development%
Oral%health%
Atypical%
Typical%
N )on%
Sleep%
D %
M %health%
E %
V %
M ) %or%
E %R %
ADHD%
T %
B %
A %
An)bio)c%
use%

Graber
90
require more experience, either experience caring for with children in general or personal
experience with a specific child and include, for example, discipline. The diamonds and triangles
in the model reflect, based on our qualitative interviews, the relative position and shape of these
topics in this continuum between expertise and experience. A diamond implies that the bulk of
information that is helpful to families lies in between experience and expertise, with areas where
either experience or expertise is needed (implied by the thinner tails of the diamond). The model
explores which type of knowledge, expertise, experience or both, most benefits a family’s well-
being or understanding of a condition or health topic. Most commonly, these health topics require
both expertise and experience, thus falling in the middle. Arguably, each of these topics and shapes
should touch both extremes of the model, and the nature of any individual relationship and
individuals’ expertise or experience could alter the shape. From our data, however, these shapes
make sense. We believe that the scope of health advice from family child care providers falls
somewhere in the middle between the extremes of experience and expertise. As family child care
providers receive more training and support, their line of scope may move farther left in the model.
Further implied in the model is the role of collaboration between those with experience and those
with expertise. Integrated care teams that include the perspective of the family child care provider
would be able to combine the child care provider’s experience with a child with developmental
delay, for example, with a health care provider’s expertise and more comprehensively address the
needs of a family. Health topics needing care coordination certainly call for integrated care teams
yet a limitation of the model is that all of the topics call for such a team. Topics that call for training
for the child care provider beg the question of who will do the training, how will it be monitored,
and to whom will providers go when they have question in general or about a specific child.

Graber
91
We believe that creating this model is important so that support, curriculum, and consistent
messaging efforts can be directed to family child care providers. This may be especially beneficial
around topics that are generally rooted in experience (such as nutrition and how to introduce new
foods to children) and could then expand a family child care provider’s expertise in this area
(including the importance of introducing a new food multiple times to a child to allow them to
accept it more readily). The model also allows a possible visual depiction of limit setting and role
definition, where further left past a certain line, family child care providers should not be giving
advice. It may be helpful to child care providers to identify areas where experience alone may not
be enough for a family, and when it is appropriate to support them in seeking help and education
from a health care provider. For example, with development, while a family child care provider
may feel very comfortable discussing typical child development with a family, if they identify a
concern for a child, such as a speech or motor delay, they should feel comfortable communicating
this concern to the family, but also know to refer the family to the child’s health care provider.
Additionally, it may be helpful to health care providers to recognize the areas where child care
providers can work with families based on their experience and expand health education and
messaging to vulnerable families. For example, for children that are obese, health care providers
could identify goals with a family and then communicate these goals to the child care provider,
who could put them into practice during the day with the child and reiterate the messages to the
family. Parents and community service providers noted the effectiveness of shared and repeated
messaging of health topics. With an acknowledgement of what areas child care providers can and
should be encouraged to share with families, including the topics more on the right side of our
model in Figure 4, health care providers have the potential to collaborate with child care providers

Graber
92
and encourage them to reiterate health messages, further potentiating a family’s willingness to
change.
Communicating about developmental concerns
Within the scope of health advice given by child care providers, development is a particularly
delicate issue. This study affirms that recognizing and communicating about developmental
concerns is difficult and amplified for families living in poverty. Parents have a “dream” for their
children and when this vision is challenged, they have difficulty letting it go. The intimate and
personal nature of this dream and its association with an individual’s ability to parent sets the stage
for disappointment, denial, anger and then guilt. The guilt is driven by the concept that the parent
could have done something to prevent the developmental delay, something reiterated by health
care providers and community service providers. Nonetheless, when seeking identification and
then intervention services, there is tension between the experience of child care providers and the
expertise of health care providers. Undoubtedly both perspectives are needed in both the
identification of developmental delay and the interventions. A multidisciplinary collaboration of
parents, child care providers, health care providers, and community service agencies may be the
best model to maximize experience and expertise for the benefit of families.
Moving towards consistent and grounded health messaging
Many health care providers and some community service providers expressed concern about the
quality of health information shared by child care providers with families. Many called for a
“standardization” of health information, verified by a federal or state body. Others wanted child
care providers to receive specific training and continuing education, so that they were regularly
updated about health topics. In Connecticut, an effective model for sharing health resources has
utilized “academic detailing,” where individuals are not only given material to share with others,

Graber
93
but also are trained in how to use it and then receive a follow-up visit from one of the trainers to
reinforce how the materials may be used. In 2010, the Connecticut Department of Social
Services wrote Connecticut’s Guidelines for the Development of Infant and Toddler Early Learning
or the Early Learning Guidelines (“ELG”), a resource binder for child care providers with succinct
important messages about development, developmentally appropriate activities and correlating
handouts for parents (81) . To obtain the ELG, however, child care providers and directors need to
attend a specific training in how to use this tool. In the weeks that follow the training,
developmental specialists then visit child care providers to follow up on their use of the ELG and
to answer lingering questions or concerns. The ELG has been received very positively in the child
care networks in New Haven and child care providers report to be using it with their parents (82)
. This model of academic detailing, the use of succinct materials, specific training, and directed
follow-up, could be especially useful in further training family child care providers as health
educators and advocates. For example, this model could be applied to teaching child care providers
about obesity, where they receive an easy to use resource book with distinct health messages, attend
a training in how to use the book and how to discuss these issues with parents, and then receive a
follow-up visit from an expert who can answer their questions and reinforce use of the tool. As
with the ELG, it would be important to give child care providers the contacts of experts that they
can call with any questions or to refer a family for further assistance.
In many ways, the model of the ELG would be able to address the concerns expressed in this study
by health care providers, parents, and community service providers that the health advice from
child care providers does not mirror advice shared from pediatric practice. Collaboration by health
care providers, community service providers, parents, and child care providers in the formation of

Graber
94
such tools would be instrumental, creating not only shared health messages, but also messages that
will be relevant and applicable to vulnerable families.
Sustainability of family child care providers as health educators and
advocates
While several family child care providers are already giving families health advice, coordinated
and comprehensive care that integrates the many individuals invested in a child’s health would
likely prove most beneficial to vulnerable families. To sustain family child care providers as health
educators and advocates, continuing education, reflective supervision, and professional
organization will be critical. These needs are mirrored in the community health worker literature:
While there is a lot to learn, there is a lot we do know about making [community
health worker] programmes work better: appropriate selection, continuing
education, involvement and reorientation of health service staff and curricula,
improvement supervision and support are non-negotiable requirements. These need
political leadership and substantial and consistent provision of resources.
(33)
Regular, consistent funding would greatly improve the training and support services given to
family child care providers in this role. Variable grant funding makes this a particular challenge.
Limitations of the study
The findings of this study must be considered within the context of several limitations. Only
English speaking parents, health care providers, and community service providers were
interviewed in one geographic region. The experiences and insights of non-English speaking
participants may be different than those expressed here, especially in regard to accessing health
and social services. Second, this study only included parents whose children were in licensed
family child care, excluding those being cared for by friends, relatives, or in center-based care.
Many children are cared for by family and friends who do not have formal training or support and
these individuals’ perspectives would benefit the development of health education and training.

Graber
95
Additionally, as a medical student conducted the interviews, social desirability bias may have come
into effect. We believe these effects to be minimal, however, as several efforts were taken to ensure
the comfort of the interview participant through establishing rapport and utilizing patient-centered
interview techniques. Fourth, as a qualitative research project, this study did not attempt to collect
objective data about the effectiveness of family child care providers as health educators. Instead,
personal perspectives were sought to provide insight into how such a role and collaboration would
work. To maintain scientific rigor, we developed our sample using thematic saturation, utilized
independent transcription, attempted to standardize coding and analysis using a interdisciplinary
Research Team, maintained an audit trail that documented the identification of our results, and
presentation to the Advisory Group for confirmation of consistency of findings (61, 83-85) .
Further, not all transcripts were reviewed by each member of the Research Team.
While great effort was taken to ensure that all transcripts were coded with the perspectives of all
Research Team members, some discrepancy in coding may have occurred. Finally, the results of
this study cannot be generalized to other populations. The characteristics of providers are provided
only to demonstrate that they reflect superficially the population from which they are drawn.
Future Directions
This research will be shared throughout the greater New Haven early education community,
introducing the role of family child care providers as health educators and advisors and further
exploring the development of specific tools and trainings, such as the ELG. Future directions for
this research could be the inclusion of Spanish-speaking parents and community service providers,
as there are a significant number of Spanish-speaking family child care providers in New Haven.
Their perspectives and insights may be different than the population interviewed in this study.
Further, other geographic regions in the U.S. could be explored for similar themes. With thematic

Graber
96
saturation of these groups, a quantitative study could explore the effectiveness of family child care
providers as health educators.
CONCLUSION
Innovative approaches to connect vulnerable families to health care and health education must be
identified. Trusting, longitudinal relationships with frequent interactions between parents and
family child care providers make child care providers ideal conduits of health education for
vulnerable families. Previously, studies had explored the perceptions of family child care providers
about their role as health educators (29-32, 54, 55) and only a few of these had begun to discuss
the scope of information provided by child care providers (29, 30, 32). Through an indepth
evaluation of the perceptions of health care providers, community service providers and parents,
this study uniquely substantiates the concept of family child care providers as health educators in
the medical literature. This study also begins to outline the practicality and limits of this
responsibility. As hypothesized, health care providers and community service providers do not
utilize family child care providers to disseminate health information currently. This study supports
the development of a public health system of health education for parents that incorporates child
care providers as community health workers. A multidisciplinary collaboration of parents, child
care providers, health care providers, and community service agencies may be a strong model to
maximize both experience and expertise for the benefit of families.

