


Defining Types of Insurance
To analyze types of health care plans, it is first important to define the
characteristics of health insurance which are found within each plan, as defined by the
National Health Interview Survey writers. For the purposes of this study, general
insurance types were broken down into five groups. The first group is the uninsured,
which is defined as those individuals who do not list that they have any type of insurance
coverage, or minimal Single-Service Plan which covers only one aspect of health care
such as dental or prescription benefits, with no other type of insurance coverage.
Individuals who qualify for Medicare are those over 65 years of age and select disabled
individuals receiving federal coverage. Medicaid is a joint federal-state program where
the state administers coverage for low income and disabled individuals under the age of
65. Military insurance encompasses TRICARE plans, Veteran’s insurance, and CHAMP-
VA plans, which cover the families of members of the armed forces. Other government
insurance includes the Indian Health Service, which is a federal program covering Native
Americans, state –sponsored health plans, which are any type of staterun coverage plans
excluding Medicaid, or any other public health care plan which is not Medicare,
Medicaid, or military insurance. The distinction is made between these other government
insurance plans and Medicare and Medicaid policies because they have very different
coverage of services. Private insurance includes those plans which are not provided by
federal or state programs, but does include Medi-Gap because it is purchased by the
individual to supplement other public plans. These private plans are typically purchased
by the individual, the employer, or the union a person belongs to. There are large

variations between private insurance plans, so this category is divided into subcategories
reflecting these differences.
The first group of private insurance includes those with HMOs, or Health
Maintenance Organizations, and IPAs, or Independent Practice Association. These are
plans which offer care to their enrollees for one fixed cost. All patients pay a monthly or
annual fee for any amount of care they receive, but they have to receive all care a
specified locations. IPAs, are similar to HMOs, but instead of linking patients to a
hospital, they are linked to a variety of independent practices with different specialties so
all care is covered. They have the same incentives for patients to receive care solely at
specified locations and therefore are grouped together in this study. The second group of
private insurance consists of PPOs, or Preferred Provider Organizations, and POS, or
Point of Service plans. PPOs are another type of managed care, but unlike HMOs, they
offer financial incentives for their enrollees to pick doctors from a preferred list, but are
allowed to go out of network for care, if they pay a higher price. POS plans also allow
for out of network coverage, and like PPOs, offer financial incentives for patients to stay
within the network for care. These two plans are similar in structure and incentives and
are grouped together in regressions. The third group of private insurance is comprised of
FFS, or Fee-For-Service, plans. Here, the insurer covers part of the hospital bill after the
service has been rendered and the individual pays the rest. These FFS plans are the
private insurance option with the greatest freedom of choice of doctor and location of
care for the patient.

These distinctions between plans are important to highlight because differences in
health care consumption, when other care-dependant variables are controlled for, indicate
the effects of incentives and disincentives within each plan. Recognizing that individuals
are induced into specific patterns of consumption is an important implication of health
care policy reform. In determining which type of insurance to encourage or dissuade
individuals from acquiring, understanding the implications inherent within each plan
allows for a more encompassing perspective on health care policy.
III. Theory and Literature Review
In studying the relationship between insurance coverage and the health and health
care use of individuals, it is important to understand the theory behind insurance and
health care consumption. One main topic concerning the theory behind insurance and
health care use is moral hazard, or the induced consumption of health care due to over
coverage by insurance. This discussion of moral hazard will be followed by a review of
the literature regarding the relationship between insurance and health care use and the
demand of insurance. These results will then be explained through an analysis of the
characteristics of different insurance plans and how they induce people to consume care
differently, and influence doctors to provide care differently immediately and in the long
term. All of these demand side issues are rooted in the idea that there is asymmetric
information between the consumer of health care and health care professionals and the
insurance providers. Another level of uncertainty resides on the supply side, between

physicians and what is appropriate care, and between insurers and patients, as health care
expenditures are attempted to be lowered.
A. Theory of Moral Hazard
With the acquisition of health insurance, the consumption of health care increases
because insurance policies decrease the price of care for an individual. Consumption
above the necessary level of care, as seen in Graph 1, is the inefficiency referred to as
moral hazard. Graph 1 depicts the dead weight loss from moral hazard with insurance.
The shaded portion represents the inefficiency of the market involving moral hazard,
assuming no co-pay or deductible. Increasing the level of coinsurance or lowering the
copayment paid by the consumer moves the individual along the demand curve, changing
the quantity of care consumed. The patient consumes more health care because, from
their perspective, they face a lower price. The demand curve is theoretically equal to the
marginal benefits for the individual at any quantity and price of health care. Curve D2
represents the demand of an insured individual. Each point on the line represents the
balance where the benefits of care equal the patient’s willingness and ability to pay for
that quantity of care. This balance is unique for each individual because the willingness
and ability to pay varies over time and from person to person. Changing the copayment
also changes the individual’s willingness and ability to pay, as shown by the sliding
downwards along the demand curve with insurance (D2). This slide down the curve from
the ideal quantity of health care consumption, X1, creates more and more waste in the
market because the marginal social cost of health care consumption is greater than the
marginal social benefit. At the point where coinsurance is zero, X2, the price of care is
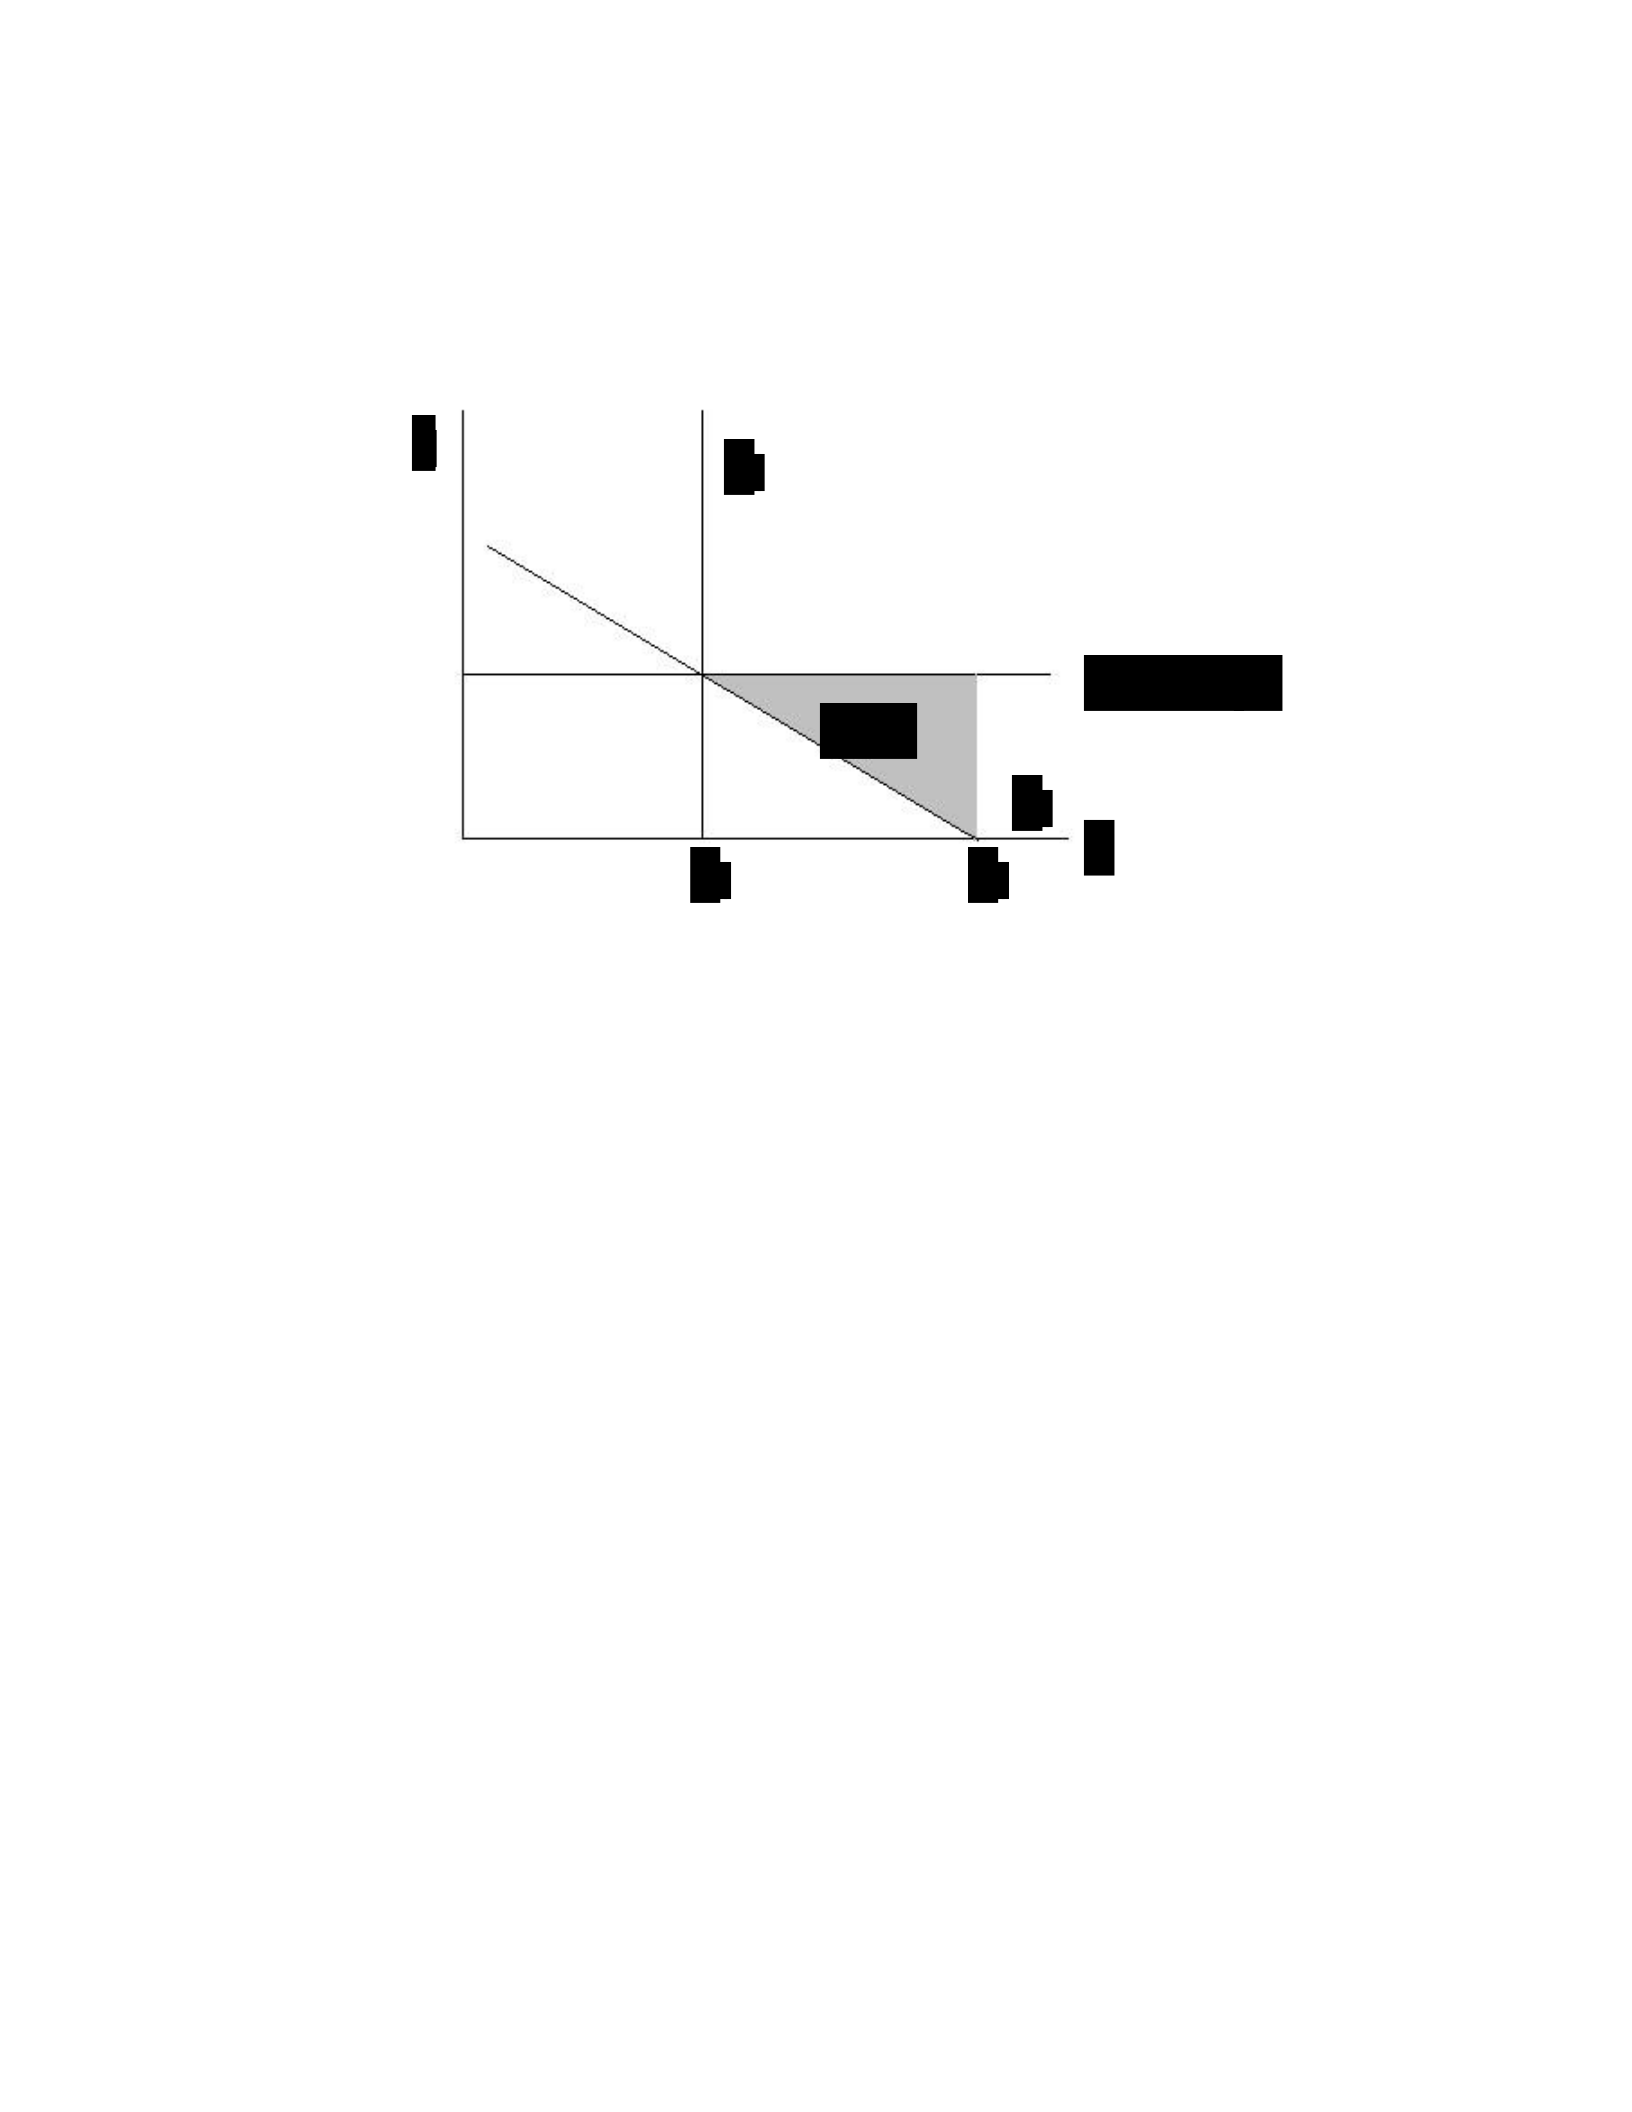
zero for the patient; at this point individuals consume the greatest amount of health care
and also generate the greatest amount of inefficiency.
Graph 1. Moral hazard causes a shift along the demand curve creating DWL, or
inefficiency because a wasteful amount of health care is demanded.
The differences in the balance between the marginal benefits and costs are
represented by the slope of the demand curve, or the elasticity of demand for health care.
If the demand curve has a steep slope (D1), or is inelastic, the price of care could change
dramatically while only inducing a small change in the quantity of care consumed.
Conversely, if the demand curve is elastic (D2), a small change in price has a dramatic
effect on the quantity of care consumed. The elasticity of demand also determines the
size of the DWL, along with the level of the co-pay. An individual with an inelastic
demand for health care will have a smaller amount of DWL than one with a very elastic
demand curve because even if the price of care is substantially lowered, they will not
consume a much larger quantity of care.
DWL
MC = Price
D
2
D
1
P
X
1
Q
X
2

In other words, when insurance is purchased, the cost of health care decreases for
the individual, causing a change in the quantity of health care demanded. For the same
market price as before, which represents true marginal costs, a patient can consume a
greater amount of health care because the insurance policy is covering part of the price of
the care, thereby lowering the cost for the patient. At the new level of health care demand
the marginal social costs of consuming health care outweigh the marginal social benefits,
creating waste.
It is hard to determine whether this increased consumption of health care due to
the acquisition of insurance is actually inefficient because this increase may represent
care which was needed, but not previously affordable. This idea of under-consumption of
care due to the inability of a patient to pay is also illustrated in Graph 2. Since the
demand curve is comprised of the patient’s willingness and ability to pay for care, if they
do not have the ability to pay for necessary care, any increase in consumption of care up
to the point where the marginal costs are equal to the marginal benefits is not moral
hazard, but a movement towards appropriate consumption of care (Nyman, 2007). It is
difficult to determine whether this increase in consumption is inefficient or a correction
from a previous lack of access to necessary health care and is assessed in this study by the
appropriateness of care measures. Those cases where an increase in consumption of care
in the short run leads to fewer hospitalizations for ambulatory care conditions (those
conditions where hospitalization is deemed unnecessary if proper maintenance care is
received), illustrates new access to necessary care; those increases where the long term
hospitalization rate is not decreased is determined to be moral hazard.

B. Literature Review
Since the size of the DWL depends on measures of consumer responsiveness to
price changes of health care, we now turn to the empirical literature which examines the
correlations between insurance and health care consumption. The literature on the
relationship between insurance and an individual’s propensity to purchase health care
falls into two major categories of studies. The first category is randomized treatment
control studies, which is characterized by a group of subjects receiving randomized
treatments or assignments of different insurance policies and another group serving as the
control. This type of study is the “gold standard” because it allows for the largest degree
of control by the experimenter over the conditions of the subjects and treatments. In
randomized treatment control studies regarding health insurance, researchers examine the
differences between health outcomes or consumption patterns of the treatment and control
groups. Because these groups were treated the same except for the variable in question,
the treatment and control groups are compared directly to examine whether insurance
affects health outcomes. The most notable randomized treatment control study is the
RAND Experiment from 1971 which will be discussed below. These studies are
expensive and time consuming and are therefore rare. The RAND Experiment is referred
to extensively because it one of few randomized treatment control studies of health
markets.
The other category of studies is observational studies, which constitute the bulk of
the literature examine in this paper. These studies take large compilations of data and
examine the traits of individuals and their health outcomes and consumption patterns.

Statistical analysis yields correlations between these variables and the probability of a
specified outcome to determine if the relationship between the two is significant. This
dataset differs from those used in randomized treatment control studies because the
outcomes are observational in nature and therefore the environment of the individual or
their treatments cannot be directly controlled. The group of individuals may be randomly
selected to participate in an observational study, but within these groups, the treatments
cannot be applied consistently because the data is being collected is the result of choices
on the part of the subjects. There is a tradeoff between external and internal validity
between observational studies and randomized treatment control experiments.
Observational studies are externally valid in the sense that they can include a very large
population of subjects from diverse areas relatively easily, but there are internal variations
between the treatments of each subject which are hard to control for. Randomized
treatment control studies are internally valid in the sense that each subject is treated
consistently, except for the variable in question, but are limited in the sense that these
studies are typically conducted on small populations in small geographic areas. Since
randomized treatment control studies are so costly to perform, they cannot be conducted
nationally and therefore may only describe the behaviors of a small subset of the
population. Both types of studies are discussed in this paper to conduct the most accurate
analysis of the relationship between health insurance and care consumption patterns as
possible.

C. Review of Randomized Treatment Control Studies
The 15 year RAND Health Insurance Experiment from 1971 to 1986 was the most
notable randomized treatment control study in the social sciences conducted in the United
States. The RAND Experiment studied the impact of generosity of insurance coverage on
health and health care use. Analysis of the RAND Experiment by affiliates of the RAND
Corporation found that cost-sharing policies such as coinsurance or copayments reduced
both the amount of unnecessary and necessary health care purchases. The goal was to
determine the optimal level of coinsurance as to reduce the level of moral hazard (Brooke
et al, 1984). In the RAND Experiment, 5809 subjects were randomly assigned to various
insurance coverage plans of no cost sharing, 25, 50, or 95 percent coinsurance rates
(Keeler, 1992).
Each family received monthly monetary “participation incentives” and a
“completion bonus” at the end of the study to decrease the level of attrition among
subjects (Newhouse et al, 2007). The level of attrition and its impact on the results was
criticized by Nyman (2007). He claimed that the findings of the RAND Experiment -that
there was a decrease in health care expenditures as coinsurance increased- were due to the
high level of attrition among subjects. He argued that those people who had high levels
of coinsurance left the study and found alternative insurance because they could not
afford their treatment. This would eliminate a large amount of health care spending
recorded in the study if those who needed to purchase health care left the experiment
before they purchased it (Nyman, 2007). Newhouse (2007) countered this argument by
pointing out the presence of monetary “participation incentives” and a “completion

bonus”. He argued that dropping out of the study was against the financial interest of
individuals because of these monetary incentives. He also drew attention to data which
shows no change in hospitalization rates of those who dropped out of the study before
and after they left. Since there was no change in hospitalization and there were no
financial incentives for any one group to drop out of the study, I find the effect of attrition
to be negligible.
Critiquing the RAND Experiment, Nyman (2007) argued that the RAND
Experiment shows both the level of unnecessary moral hazard experienced by increasing
the level of insurance for consumers, as well as the level of health care the insured will
now consume because they gained access to previously unattainable care. This latter
variation of moral hazard, Nyman argued, is beneficial to the population and represents
an increase in welfare. This original premise, that the increased level of moral hazard
would have a large effect, is debatable because health care is shown to be generally
inelastic, so any increase in moral hazard would be small. The impact on the welfare of
individuals who reduced health care purchases is also debatable. In Keeler’s analysis of
the RAND experiment, he attributed the decline in blood pressure control, corrected
vision, and oral health to increased cost sharing, but stated that there are no other negative
health effects (Keeler, 1992). Other reviews of the RAND Experiment explained that
there was no change in the health of individuals with various coinsurance rates except for
those with low incomes (Normand, 1994). This could be explained by the ability of those
with high incomes to compensate for high coinsurance rates because of their increased
ability to pay for health care. They offset the increased cost for care caused by a lower-

coverage insurance policy with their own expendable income and therefore it would have
been interesting if the RAND Experiment had analyzed whether the rate of health care
was the same between insurance groups, indicating that these people just spent more of
their own money for care instead of relying solely upon the insurance plan, resulting in
negligible differences in health outcomes between groups.
A downside of the RAND Experiment is that the data was collected in the 1970s
and 1980s, over a quarter of a century ago. The themes of this research may hold true
over time, but the realm of health care and insurance has changed significantly since then.
For instance, there are now many different insurance types such as PPOs, HMOs, and
HSAs which were not considered in that study. The health care community would benefit
from another study such as the RAND Experiment to incorporate the various new
insurance options. This type of experimental study is very expensive, so in this paper,
observational data was utilized.
D. Review of Observational Studies
The other branch of literature examined falls under the scope of observational
studies. These studies lack the ability to control the treatment of individuals, because the
measured outcomes are the result of individual decisions by the subjects. But,
observational studies do allow for large numbers of respondents with few negative moral
implications because an authority is not assigning on possibly beneficial or harmful
policies because the treatments have been essentially self assigned. One such
observational study conducted by Goldman et al (2007), looked specifically at the
influence of coinsurance rates on prescription drug spending found that with every ten

percent increase in coinsurance rates, there was a two to six percent decrease in the level
of prescription drug spending. They also associated increasing coinsurance rates with
decreased treatment with drugs, and increased risk of discontinuation of care by patients.
This decrease in treatment with drugs could be beneficial because there would be less
over-prescription of antibiotics and unnecessary medications, and also that doctors would
prescribe the generic form of the drug, changes which decrease medical costs. The article
stated that the welfare benefit is unknown because there could also be a decrease in health
in the long term if patients do not take necessary drugs prescribed to them due to
prohibitory coinsurance rates. It would be difficult to determine the long run cost of
declining costly prescription medications, because it is hard to directly link any illness as
the effect of the decrease in prescription drug usage. This is exemplified in Graph 2 by
shifts in demand curves with and without insurance.
The demand for health care is based on the marginal benefit of consuming an
additional unit of health care, or the patient’s willingness and ability to pay. The
insurance effect is the impact on the quantity of care consumed with insurance. Health
care and health insurance are not typical goods. There is an equity issue associated with
access to quality health care which rests on the premise that individuals should have
access to health care no matter their financial situation, similar to the idea of access to
education. It is very important for health care to be provided to everyone because there
are many positive externalities associated with health care. A healthy population is able
to be an efficient workforce, and since productivity is social, quality health care has a

positive social welfare effect. There are also the benefits derived from the altruistic want
for everyone to have access to quality health care (Sen, 2004).
When individuals are uninsured, their ability to pay or ability is less than the cost
of care, leading to dead-weight-loss (labeled DWL A) or inefficiency because they are
under-consuming health care. Normally, a lack of ability to pay for a good would not
cause this shift in the demand curve, but low income individuals are also constrained by
credit because it is difficult for them to obtain loans and credit to pay for health care.
These individuals are missing out on care where the true marginal benefits exceed the
marginal costs of care. This is illustrated in Graph 2 by the left most demand curve with
the associated loss of marginal benefits to the patient shaded in grey. The uninsured
individual consumes the quantity X1 of health care which is less than the most efficient
quantity of health care consumption, X2. The under consumption of prescription drugs
discussed by Goldman et al (2007) would be illustrated by the Dno ins curve, because
individuals are not consuming necessary care. The demand curve with the true marginal
benefits of care (MBtrue), or middle curve on Graph 2, represents the most efficient level
of insurance, or where the price of care is equal to the marginal benefits of care
consumption for each patient.
On the other hand, when coinsurance rates or co-payments are too low, the price
of health care is artificially lowered from the perspective of the patient and they are
willing to purchase more health care at this lower price. This shifts the demand curve out
because a patient’s ability and willingness to pay for care at this lower price has
increased. Since the demand curve also theoretically illustrates the marginal benefits of
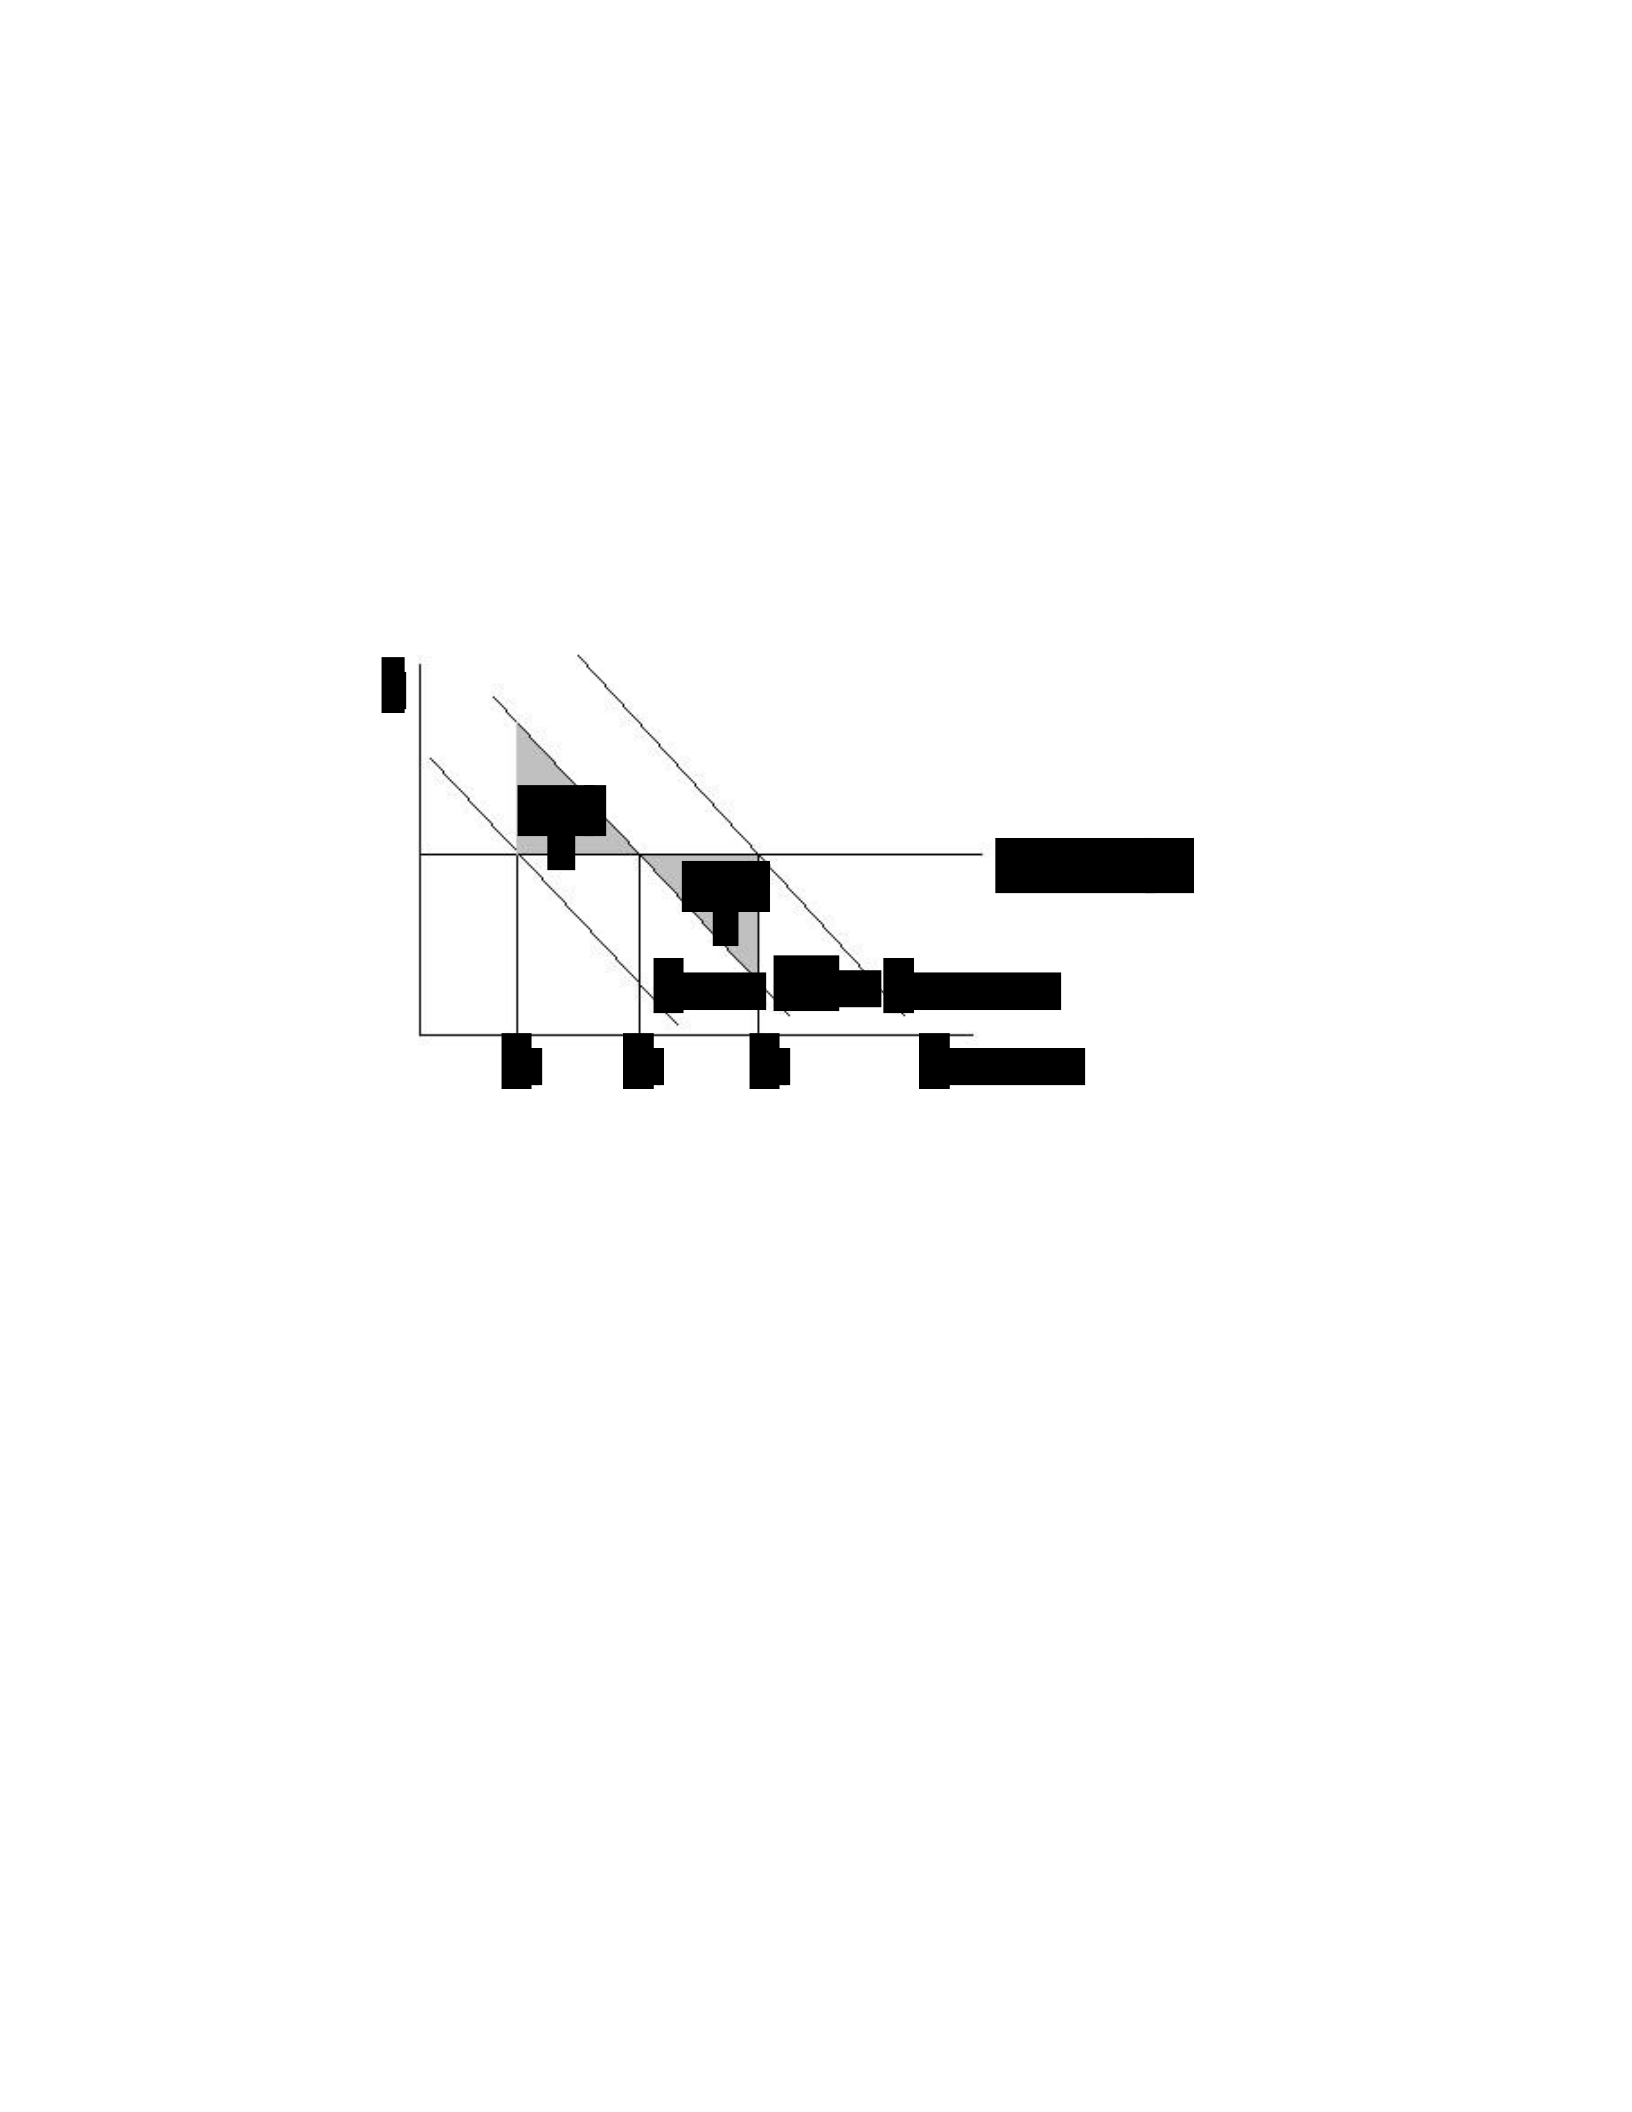
consumption, a higher demand curve than the “true” level of demand articulates that the
marginal benefits are not maximized at this level of demand. Patients then consume the
quantity X3 of care again generating dead-weight-loss (labeled DWL B) because the
marginal costs of care far exceed the marginal benefits of care for the patient but they are
still consuming care because it is at a low dollar cost to the individual, but taxing on the
overall system (Graph 2).
Graph 2. The insurance effect causes under consumption of care if patients do not have
enough insurance and over consumption of care if they are over insured.
Levy and Meltzer (2007) assert that the causality established by other studies may
not be due to the effect of health insurance on health, but instead reflects the presence of
unobservable factors. These authors’ findings are consistent with the RAND study
analysis, stating that, “health insurance certainly increases the quantity of health care
consumed,” (Levy and Meltzer, 2007) but they go on to show that individuals receive less
marginal benefit for each additional unit of health care consumption, despite this increase
in spending. This article attempted to determine which policy will be the most
costeffective and beneficial for the public to increase insurance coverage to a greater
MC = Price
D
over insured
MB
true
D
no ins.
DWL
B
DWL
A
P
Q
Health Care
X
3
X
2
X
1

portion of the population while maximizing marginal benefits. When discussing marginal
social costs and benefits, we are mainly referring to the effects on the individual and
society of consuming more care. Society benefits from people being disease-free and
healthy enough to work, but incurs a cost when the scarce resources of health care are
consumed because of the fixed supply of health care. Individuals benefit from consuming
health care, but after a certain level, the marginal benefits of consuming an additional unit
of health care diminish and it is no longer efficient to consume more care past this level.
There is also uncertainty in determining the true marginal benefits of care. It has
been shown that there are similar, or even worse, health outcomes with higher health care
spending when comparing cities of similar demographic composition (Gawande, 2009).
The reason we see under and over consumption of care is partly due to the fact that we do
not know what the ideal level of health care consumption should be. We are unsure of the
true marginal benefits of varying procedures as well as the true marginal benefits of each
dollar spent. This uncertainty prevents us from promoting ideal health care consumption
and should be probed in further research because there are massive efficiency
implications if this ideal level can be determined.
Since there is a decrease in demand for health care from increasing the
coinsurance rates, we must look at whether this decrease in demand has any effect on the
market price of medical care. The rising net cost of health care is a concern in the health
care industry and finding a way to manipulate the market price of health care would be
beneficial. Unfortunately, analysis on the topic of the effect of coinsurance and overall
medical expenditures concludes that there would be little to no effect on the price of

medical care by increasing coinsurance rates. In reality, the marginal social costs, or
supply curves, are not horizontal as depicted in the graphs for simplicity. Despite the
change in demand, which is elastic, by consumers with higher coinsurance rates, the
supply of medical care is very inelastic and therefore the price will not change in the long
run (Arrow, 1973). This brings us to the short run and long run cost analysis regarding
different insurance policies.
E. Cost Sharing and Deductible Analysis
In the short run, the deductible faced by the consumer plays a large role in
consumption of care because it dictates the price of care. A deductible is the amount of
money a person must spend per year before an insurance company will step in and pay
the remainder. The size of the deductible is depicted as the distance from points A to B
on Graph 3. A very low deductible (A1 to B1) encourages people to spend the small
amount of money quickly and then consume a large amount of health care because the
remainder of care expenditures cost nothing monetarily from the perspective of the
consumer. This can lead to inefficiency, as depicted in Graph 3.
Graph 3. Marginal costs and benefits of spending a CDHP deductible from the
perspective of the consumer. MSC is marginal social costs.
X
Y
P
Q
P
P
Q
Q
X
Y
No Deductible
Y
Small Deductible
Ideal Deductible
MSC
MSC
MSC
D
D
D
Q
n
Q
s
Q*
A
1
B
1
B
2
A
2

The demand curve represents the willingness and ability of the patient to pay, the
horizontal line the marginal social costs of care, or the market price, and the dashed line
the level of premium or deductible the patient faces. The shaded triangle above the
dashed line (X) is the marginal costs to the individual of spending the deductible and
consuming additional care at zero cost, and the shaded triangle below the dashed line (Y)
represents the marginal benefits of spending the entire deductible. In other words, from
points A1 to B1 in the small deductible panel, the individual pays the full marginal social
cost, and then after point B1 the individual consumes to the point Qs to maximize
marginal benefits. The dollar value of the personal loss from consuming from A1 to B1 is
“X” and the dollar value of the personal gain from consuming from B1 to Qs is “Y”. If
YX < 0, the consumer does not spend the entire deductible because they would not
receive enough marginal benefits from additional care consumed at zero cost to
compensate for the cost of the entire deductible. Conversely, if Y-X > 0, the consumer
spends the entire deductible because they would receive as much care as they wanted at a
low cost because their deductible is easily met. This is represented by the Small
Deductible graph because the marginal costs of care are easily overcome and unnecessary
care is consumed. The ideal level of deductible should be where X = Y so that the
marginal costs and benefits of spending the entire deductible are equal for the consumer.
Making the consumer more responsible for the costs of health care introduces a
new cost-benefit analysis from the perspective of the patient. Consumer-Driven Health
Plans, or CDHPs, set high premiums or deductibles and the patient must weigh their
marginal benefits of care against the costs up to a certain point, but after that deductible

has been met, the cost of additional care moves to zero, artificially changing the cost of
care from the perspective of the patient. With CDHPs, patients can chose where and
when they consume health care, but they bear more of the costs themselves. CDHPs have
been found to reduce total health care expenditures compared to managed care plans, but
in the long run, they are found to have higher costs per hospitalization admission (Parente
et al, 2004). The goal of CDHPs is to facilitate competition between health care
providers by giving the patients control over their health care spending. This market-
based approach to health care provision encourages consumers to cut costs by giving
them a financial stake in their health care. The intention of CDHPs is to reduce moral
hazard by making patients face the full marginal costs of their own health care. Fee-for-
service plans and other plans which detach the patient from the financial side of health
care, give incentives for consumers to be indifferent to costs (Callahan, 2008). Putting
the patient in control of their own health care spending reduces short run costs because
the patient has fewer visits to the doctor. CDHPs are included in the “other private”
insurance category among other insurance types for the purposes of this study so it is
difficult to derive any direct conclusions about CDHPs with these regressions.
Examining both inexpensive short run and costly long run care is crucial in identifying
efficient insurance systems.
F. Managed Care Analysis
Another type of health insurance policy, HMOs or Health Maintenance
Organizations, uses a different combination of patient-directed and provider-directed
mechanisms to effect spending than CDHPs. HMOs use three main mechanisms for

reducing health care spending: gate-keepers, capitation, and promotion of preventative
care.
Gate keepers refer to the practice of HMOs to have each patient first be seen by a
primary physician, or “gate keeper”. This procedure reduces costs because primary
health care is less expensive and it often eliminates the need of seeing a specialist, which
is much more costly (Fang et al, 2009). Since the patient pays the same amount, there are
incentives for the hospital to create access to inexpensive care so that future, more
expensive, hospitalizations and specialist visits are avoided. Forcing primary physicians
to become restrictive gatekeepers may cut costs, but may also have a negative effect on
the moral authority of doctors. The role of a gatekeeper can either be a physician who
efficiently identifies which specialist a patient should see and what kind of care they
need, or a physician whose sole purpose is to decrease costs by limiting access to care
which may be necessary (Starfield 1992, Manson 1995). This distinction is hazy because
both roles are assumed by the gatekeeper; they are responsible for directing patients to the
most cost-effective route of care. Whether this route is also the one of highest quality of
care is currently being questioned as our health care system evolves and as HMOs steer
away from the incentives which generate very restrictive “gatekeeper” primary
physicians.
Capitation is when an HMO or Preferred Provider Organization (PPO) decreases
costs by instituting financial disincentives to provide more care. If a primary doctor is a
part of an HMO with capitation policies and they refer the patient to a specialist or order
an expensive test outside of the standard procedure for these symptoms, they may not be

reimbursed as highly for the visit or may incur some other financial disincentive. These
policies reduce incentives for induced demand, or treating patients more frequently or in
more costly ways than necessary to increase their own incomes.
Emphasizing preventative medicine is a method used by HMOs to limit the
instance of costly hospitalizations in the long run. Literature suggests that HMOs induce
the patient to seek frequent preventative care visits because the consumer pays one price
no matter how much care they receive. Although they frequent the doctor more often,
their overall costs in the long run are lower than with other plans because they are less
likely to need to undergo expensive, longer hospitalizations in the future. It was found
that a 10 percent increase in HMO market penetration decreases hospitalizations for
ambulatory care conditions, also known as preventable hospitalizations, by 3.8 percent
(Zhan et al, 2004). Ambulatory care conditions are those conditions for which
hospitalizations are avoidable if proper preventative care had been received.
Reasons for admission of a patient into a hospital are grouped into three categories
in studies analyzing hospital use. The first group consists of those conditions where the
outpatient care received has little to no effect on whether the patient is hospitalized.
These are conditions for which preventative care has little impact on outcome. Another
group encompasses those conditions which are not considered to require hospitalization if
effective preventative or maintenance care is received, also called ambulatory care
sensitive conditions. The third category is referral-sensitive care such as expensive
surgery or diagnostic tests requiring advanced technology (Billings et al, 1993).
Hospitalization for conditions considered to be ambulatory care sensitive, is an indicator
for problems with access to primary health care (Millman, 1993). A list of ambulatory
sensitive care conditions (ASCH) can be found in Laditka et al (2003).
It has been found that those with HMO plans demand less hospitalizations
indicating that their demand of different types of health services varies from those with
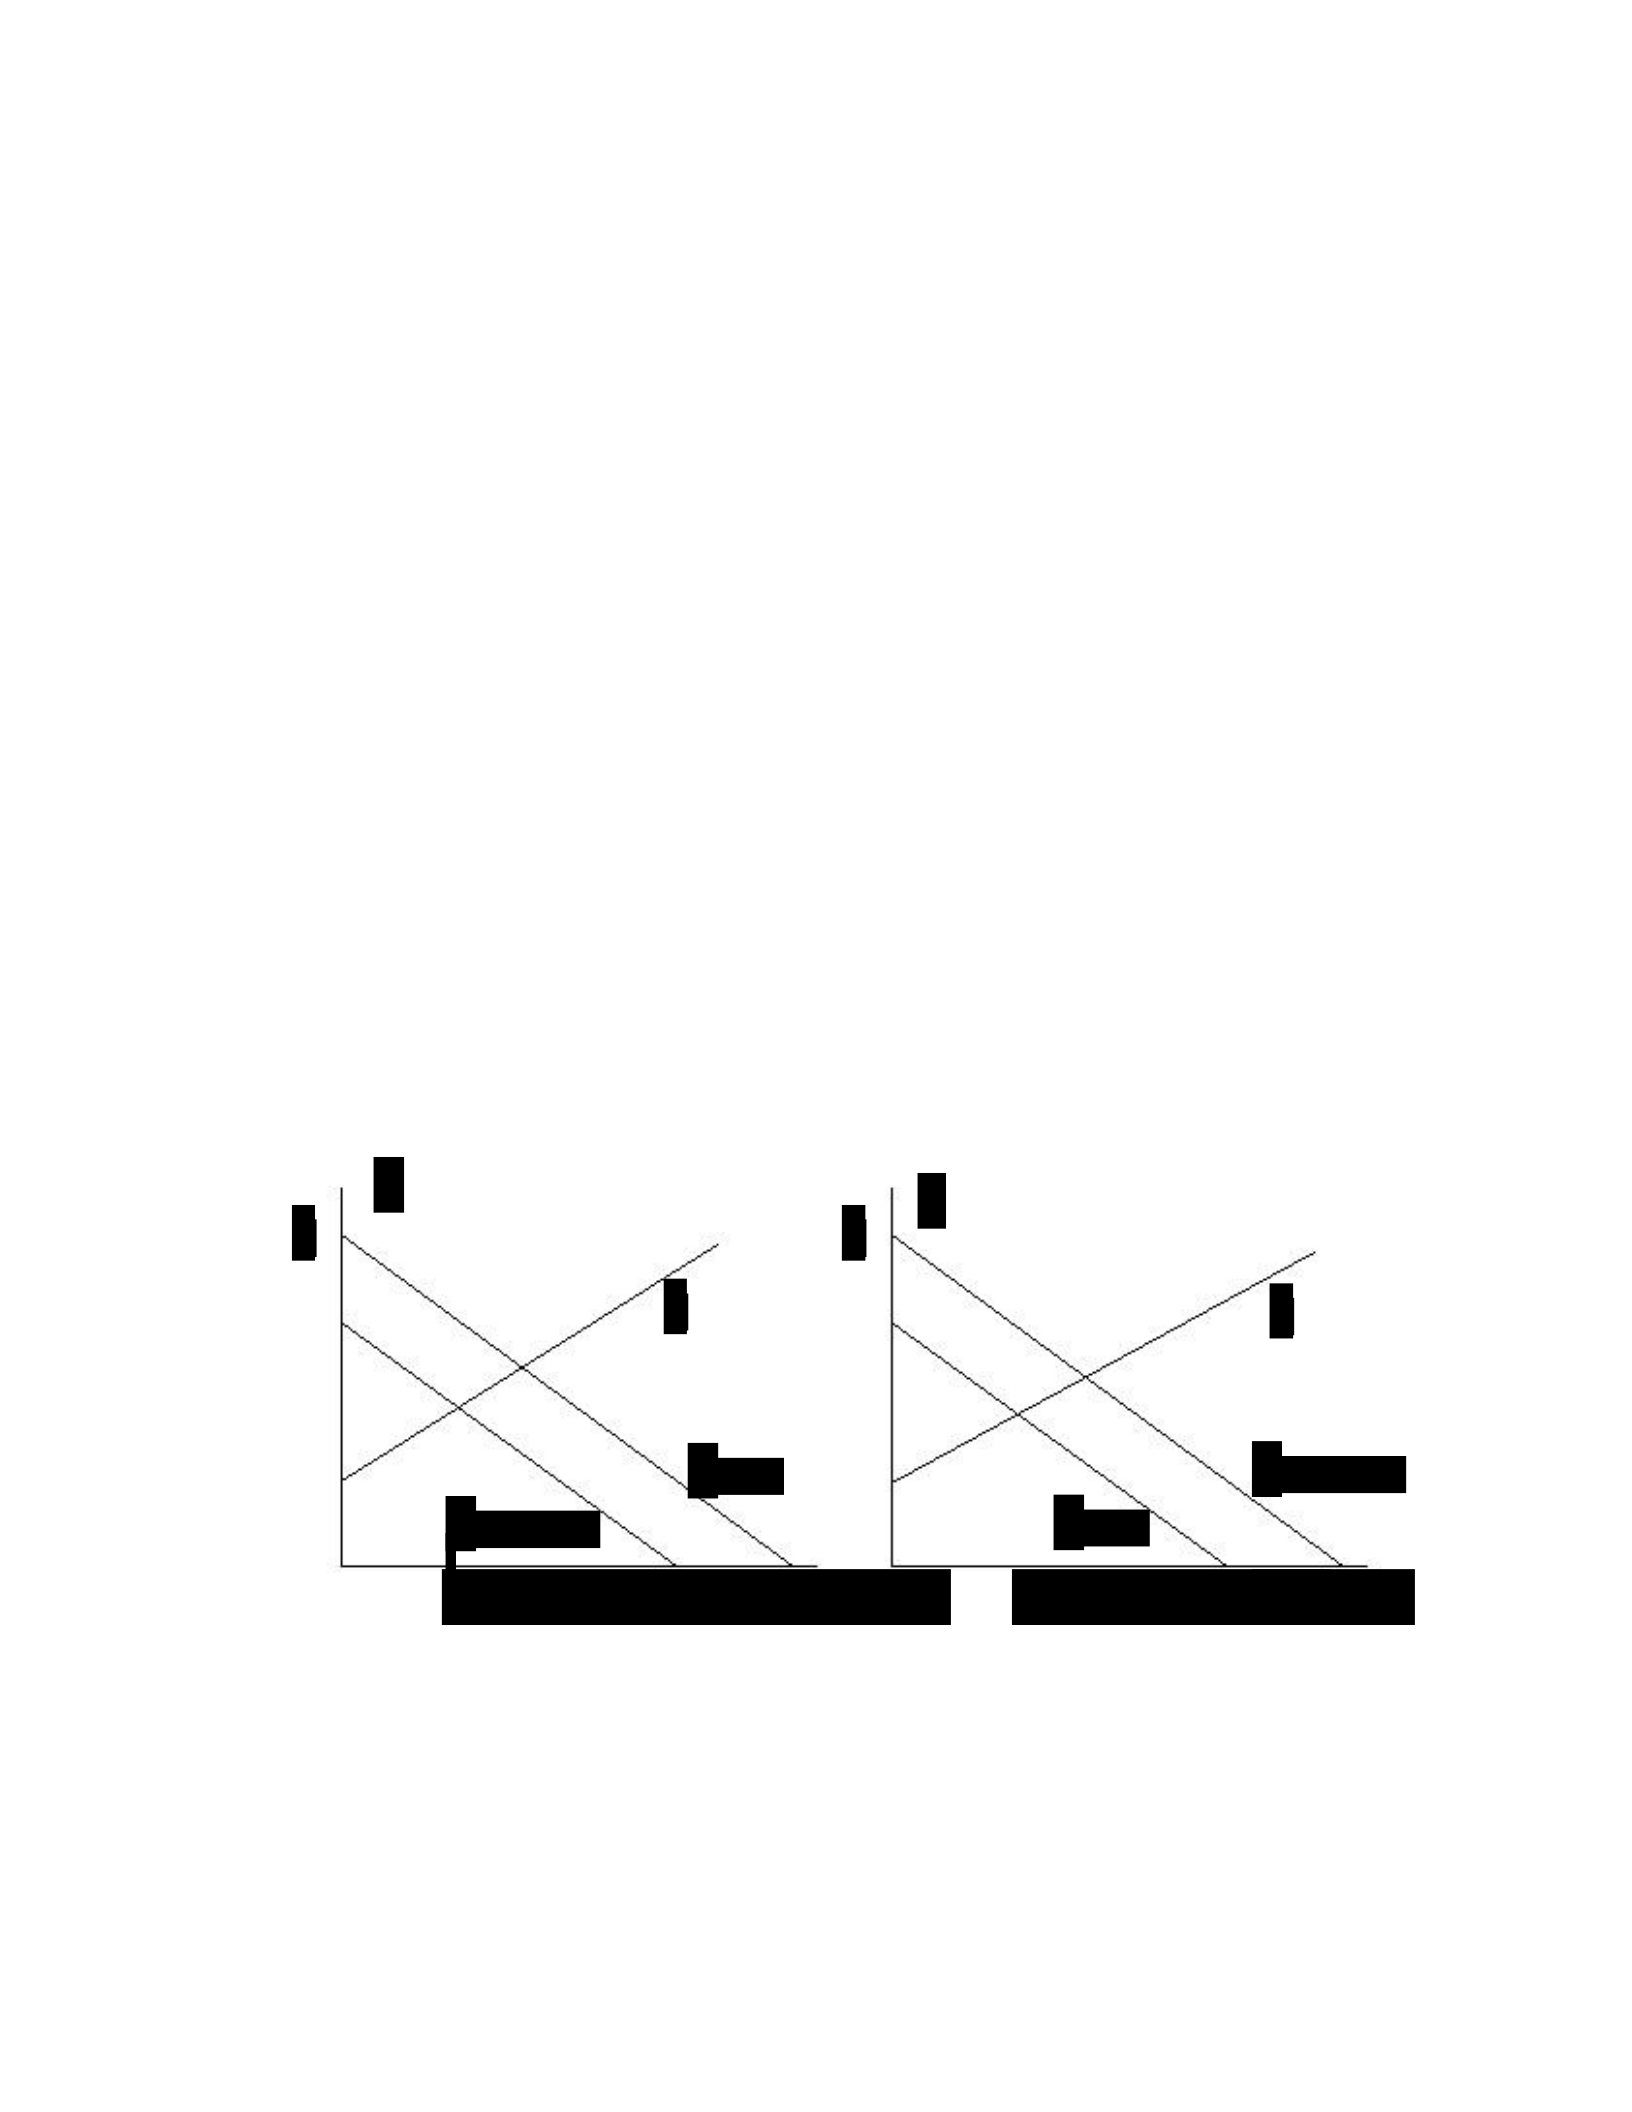
other plans (Zhan et al, 2004). Graph 4 illustrates the difference between the demand
curves of patients with non-HMO and HMO insurance policies. Panel A shows that
patients with non-HMO insurance plans demand less preventative care and those with
HMOs demand more preventative care because of the incentives inherent within those
plans. This trend of an increased consumption of preventative care in HMOs could
explain the lower rate found in literature of expensive hospitalizations. Panel B shows
that HMO insured individuals consume are hospitalized less than those with non-HMO
plans. This change in the quantity demanded of each type of care saves costs in HMOs
because preventative care is much less expensive than hospitalizations.
Graph 4. Side-by-side preventative care and long run hospitalization demand curves for
HMO and Non-HMO plans.
D
Non-HMO
D
HMO
D
HMO
D
Non-HMO
P
P
Quantity of Preventative Care
Quantity of Hospit
alizations
S
S
A
B

A study by Deb et al (2006) shows that those in HMO plans go to the Emergency
Room 90 percent more often and have 90 percent more doctor’s visits than those with
non-HMO plans. This is a surprising result, because it is inefficient for a health care
provider to have their patients frequent the ER. This could indicate a large source of
inefficiency in the way HMOs provide care. Their plans do not create incentives for the
patient to distinguish between ER and doctor’s office care and therefore the patient
chooses the immediate care option, which is the ER. This increase in doctor’s visits may
be the result of the emphasis on preventative care and would be the reason hospitalization
for ambulatory care conditions decreases in the long run, thereby decreasing costs.
Although there is certainly evidence for cost containment by HMOs during the
HMO “boom” from 1990-94, since then, those policies enacted by HMOs which were
most successful at cutting costs have been rescinded due to decreased patient satisfaction.
Decreasing the restrictive aspects of HMOs has lead to a decrease in their efficiency and
now HMOs have limited cost-cutting effects. This decreased efficiency of HMOs in
terms of cost-containment may continue until HMOs are no longer more efficient than
other sources of insurance, so policies which encourage employees towards managed care
plans, may not have the same degree of a desired effect as they did in the 1990s (Shen
and Melnick, 2006). A study of for-profit HMOs and non-profit HMOs found that the
quality ratings of non-profit HMOs were much higher than for-profit HMOs. The article
attributed this difference to the incentive of for-profit HMOs to restrict and “skimp” on
health care for its members (Burkey et al, 2008). The article concluded with the idea that
HMOs are the only way to guarantee health care but the quality of said health care is

variable. Studies have shown low physician satisfaction with HMOs, articulating the
belief that the patient receives a lower quality of care (Christianson et al, 2005).
Although HMOs may have issues, such as decreased patient and physician
satisfaction (Christainson et al, 2005), with their mechanisms to cut costs, they are
effective in doing so. Efficiency analysis shows that areas with greater HMO penetration
have a negative correlation with inefficiency, illustrating that HMOs decrease costs. The
source of the restriction of costs is unknown, but could be attributed to cutting access to
health care for patients and decreasing the quality of care, but increasing the overall
efficiency (Rosko, 2001). These mechanisms are relatively effective because they work
on both sides of the equation, they induce patients to consume inexpensive care, and they
encourage physicians to treat patients more efficiently, a topic which is discussed in the
next section.
G. Supply of Health Care Analysis: The Doctor’s Side
Physicians may not have consensus on what is considered “appropriate” care. In
many cases, there is no set course of treatment for doctors and this independence of
health care provision allows for a great deal of uncertainty but grants the ability for
treatment to be tailored to each patient. Uncertainty of which treatment is best for each
patient is a factor which is hard to account for in regressions because it pertains to the
physician’s training, overall medical knowledge, and level of risk aversion. Even with
the best training, doctors are still met with the uncertainty of what is the actual best
treatment for the patient. The general lack of evidence based medicine forces us to rely

heavily on the preferences of individual doctors which are affected by a variety of factors,
including risk aversion and possibly supplier induced demand.
A prime example of the discrepancies in health care provision is discussed in an
article by Atul Gawande (2009). Gawande compared two small Texas towns, McAllen
and El Paso, and found that McAllen had Medicare expenses of $15,000 per enrollee
whereas El Paso had expenses of only $7,504 per enrollee. This was an astounding
difference for two towns of very similar socioeconomic and demographic statistics. This
huge variation in cost of health care was attributed to general overutilization of expensive
health care with no benefits of better health outcomes or higher quality of care. Gawande
states that a patient coming in for the first time with pain from gallstones would have
once been prescribed pain medication, and told to change their diet and be sent home,
now “McAllen surgeons simply operate.” This is an easy solution for possibly
noncompliant patients, but it also generates $700 more revenue for the physician
(Gawande, 2009). It has been shown that states with the highest levels of Medicare
spending actually had lower quality of care rankings than many other states (Baicker and
Chandra, 2004). The high costs give patients more care, but not necessarily better care.
Fisher et al (2003) from Dartmouth’s Institute for Health Policy and Clinical Practice
found that these patients were receiving very expensive care and not receiving
preventative care, and also had longer ER wait times. Not only were the patients
receiving a poorer health outcome at this higher price, but they were not even receiving
basic preventative care.

Uncertainty and variability also arises from variation in the reimbursement of
doctors and hospitals by different insurance plans. These fluctuating reimbursement rates
may alter incentives to prescribe or provide certain services to patients. It is hard to
determine whether the outcome of a certain treatment pattern is due to the choices of the
consumer or the provider of health care because there are no data in this survey about
doctor’s choices except their final treatments. But, controlling for insurance type and
premium captures some of this effect.
Gawande speculates that doctors in McAllen provide more expensive care to
increase their revenues, as an illustration of supplier induced demand. With decreasing
rates of reimbursement from the uninsured and public insurance plans, the doctor or
hospital could make up for this difference by providing more expensive care. A doctor
can induce care by directly prescribing more tests or visits, and a hospital can induce care
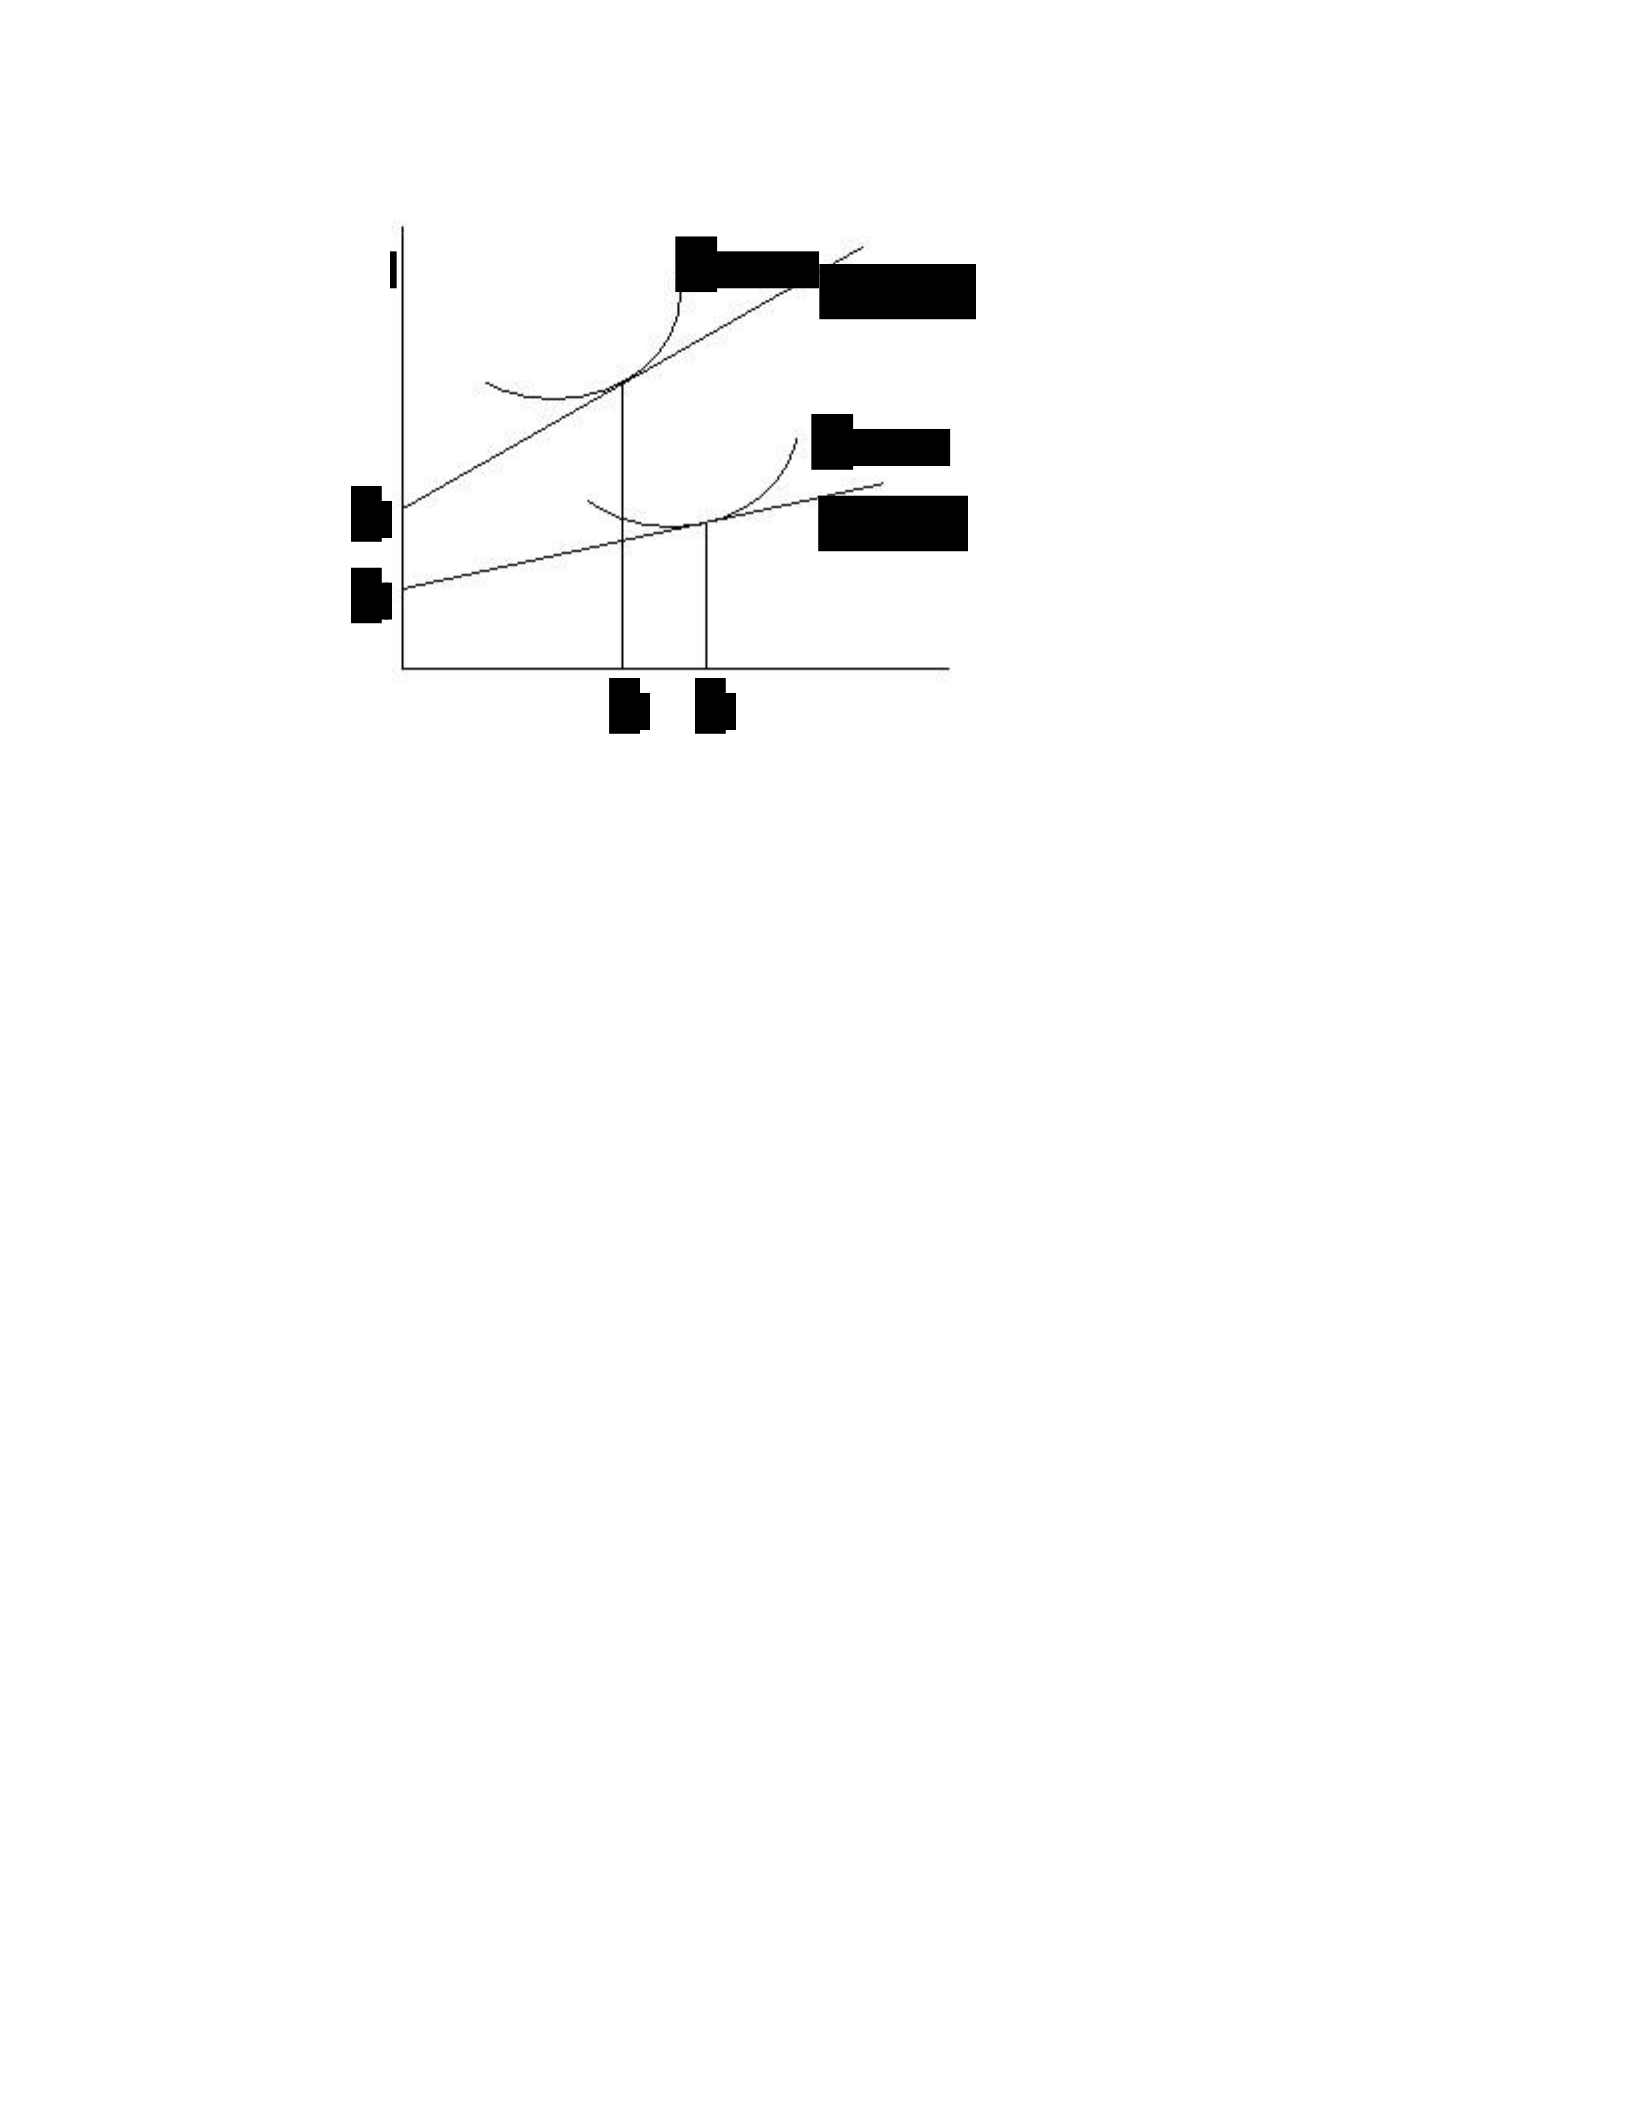
by instituting policies which pressure doctors to over-treat patients. This is illustrated in
Graph 5 by an increase in quantity of health care consumed at the low fee relative to the
higher fee.
Income
Q of Induced Health Care
Graph 5. Supplier induced demand causes physicians to prescribe more expensive
treatments increasing the costs of care.
The downward shift in the amount of income received per unit of health care
delivered is represented by the lower y-intercept and less steep slope of the Low Fee
curve. The y-intercept values, A1 and A2, represent the income of the physician if no
health care was induced, which is the point of appropriate quantity of health care. At the
lower fee, the intercept (A2) is lower than the intercept with the higher rate (A1) because
the income of the physician is lower with the low fee. The increase in supply of care seen
above (shift from X1 to X2) due to a decrease in overall reimbursement rates creates waste
just as the change in demand did as discussed earlier. The shape of the indifference
curves (IC curves) represents that doctors gain disutility by inducing more health care
consumption. This means that they need more income to make up for losing utility from
each additional unit of health care they induce due to the income and substitution effects.
If the income of the doctor is decreased by lower fees, they compensate by providing
more expensive treatments (substitution) or increasing the quantity of care supplied.
IC
High Fee
IC
Low Fee
High Fee
Low Fee
X
1
X
2
A
1
A
2

This concept can be linked to the lower rates of reimbursement from Medicaid.
Theoretically, since the rates are lower, physicians and hospitals could induce care from
these patients to compensate for this cut in reimbursement. This is a situation where it
may actually reduce overall costs if Medicare and Medicaid reimbursement rates were
increased. This is a complex topic which merits further examination because it would be
necessary to probe the market to determine the point at which the lower reimbursement
rate is still high enough that doctors and hospitals do not induce care.
In the case where the low fee causes SID, the marginal social cost of health care
consumption is greater than the marginal social benefit. This inefficiency is caused by a
supply-side shift in the market, instead of a demand-side shift as seen previously by
deductible and co-insurance variation. We are limited in that we can only measure the
final consumption patterns in relation to different insurance types, which indicate the
presence of incentives or disincentives, but cannot tell us whether these patterns are
caused by supply or demand side factors. Despite the primary origins of inefficiency,
they all result in the overuse of expensive health care and therefore we should work to
find and resolve these issues.
H. Efficiency Implications of Health Care Overuse
The increasing inefficiency discussed throughout this paper has severe
implications for the state of health care. One major source of inefficiency results from
the overuse of Emergency Room visits because of the high cost for hospitals to provide
round-the-clock care. Zuckerman and Shen (2004) illustrated the significance of the
growing burden on ERs across the United States. They explain that visits to ERs

increased 20 percent between 1992 and 2001, while this increase was not matched in
creating more ERs. Instead, the number of ERs fell 15 percent during this same time.
Due to this inadequate amount of ERs with rising ER utilization, any plan that generates
incentives to visit the ER should be deemed inefficient. With long waits and not enough
beds for patients, the ER is an extremely inefficient location to consume health care, both
in terms of the opportunity cost of the patient’s time, and the burden on the ER itself of
being over utilized. More doctor’s office visits rather than ER visits might yield lower
overall marginal costs for the same care.
There has been found to be a positive correlation between public health care plans
such as Medicare and Medicaid, and inefficiency, but this increase in cost per admission
could be attributed to an increase in PPS payments to urban hospitals in the 1990s
(Rosko, 2001). Contrary to popular belief, the uninsured are not the largest population
which utilizes the ER. Only 15 percent of ER use is from the uninsured, and the
uninsured are just as likely to be frequent users of the ER as the privately insured
(Zuckerman and Shen, 2004). Zuckerman and Shen (2004) also found that those with
public insurance were 2.08 times more likely to be frequent users of the ER, the most
likely group to visit the ER. This level of ER utilization is a focal point of this study
because of the high degree of inefficiency caused by over utilization of the ER.
Emphasizing research energies on efficiency implications of different policies is essential
to determining which aspects of current policies should be preserved and removed in the
process of health care reform.

IV. Data
The data source utilized in this study is the National Health Interview Survey from
2006. The respondents were restricted to the noninstitutionalized population 18 years of
age and older form all 50 states, but the respondents also answered questions regarding
their children. The NHIS 2006 has a sample size of 75,716 in the Sample
Adult Level with 36,561 (48.29 percent) of the respondents being male and 39,155 (51.71
percent) of the respondents being female. The insurance status of the individual was found
under the Family Level section of the questionnaire and their consumption of medical care
was found under Sample Adult Level questionnaire. The information from the files was
merged to form the data set that will be examined in this study. The policy differences
between groups, SCHIP for children, and Medicare for the elderly, impact health care
consumption and therefore age is controlled for.
A. Level and Appropriateness of Care Measures
Quantifying aspects of the health care market such as quality of health care, access
to care, and appropriateness of care, is also very complicated. The health status recorded
in the interview survey is self-reported, and is reported as: excellent, good, fair, and poor.
These four categorical variables do not leave room for a continuous scale of health status
and therefore may limit some of the conclusions which can be drawn from linking health
status alone to another variable. These broad categories are crude approximates of true
health status and therefore may not capture the true health status of an individual. Quality
of health care is also often self-reported leading to a bias because there is no standard
which each individual is using to assess the overall quality of care, so health outcomes are

used instead to indicate the quality of care received. Access to health care is also difficult
to quantify. Access can be measured in terms of distance to the nearest hospital or by
asking the respondent if they did not consume necessary health care for any reason. In
this study, the latter was used because the distance to the nearest hospital, Emergency
Room, or clinic was not recorded.
Whether an individual received standard vaccinations illustrates the provision of
basic preventative care. The relationship between the types of insurance coverage and
choosing not to get health care or prescriptions for financial reasons establishes the effect
of insurance on consumption of necessary health care. This study uses hypertension,
asthma, diabetes, bronchitis, heart disease, heart attack, and angina, as indicator variables
for ambulatory care sensitive conditions and the presence of these conditions paired with
high hospitalization and ER utilization rates indicates inefficiency. The patient’s usual
location of health care was also examined in terms of whether the patient sought out
health care at the appropriate location. Doctor’s offices or outpatient clinics were deemed
to be appropriate usual locations of care and the ER and free clinics were tagged as
inappropriate locations of usual care because of their high financial toll on the provider.
The frequency of doctor’s visits, ER visits, hospitalizations and surgeries shows the
degree to which the different locations and types of health care consumption are utilized.
Definitions of all variables can be found in Appendix 1 and the means for the full sample
and measured sample can be found in Appendix 2.

V. Methods
This study examines three hypotheses regarding how insurance policies impact
health care consumption. The first hypothesis is that basic plans such as Medicare,
Medicaid, and other government insurance will have higher rates of hospitalization and
surgery because they do not emphasize preventative care, while HMOs and other types of
private insurance will have lower rates of hospitalization and surgery. The second
hypothesis is that those with Medicare, Medicaid, and other government insurance plans
will frequent the ER more and the doctor’s office less than those with other private
insurance. The third hypothesis is that individuals with public insurance plans (Medicare,
Medicaid, and other government insurance) will list the ER and free clinics as the
primary location of health care more often than the uninsured or other private plans which
will list a doctor’s office.
There are difficulties in measuring the relationship between health care use and
health insurance as described by Levy and Meltzer (2007), including the omitted variable
bias inherent in the relationship between health insurance and health care use. Omitted
variable bias is when the variable in question is also correlated to other, unknown or
unmeasured, variables which bias the regression coefficient. As many control variables
as possible are included to minimize omitted variable bias, but some bias may remain.
Controlling for geographic region, place of birth, and race, accounts for some of the small
area variations throughout the nation. Education, sex, marital status, income, age, and
self-reported health status will also be controlled for in all regressions. The Grossman
model indicates that education and income have large effects on consumption of care and

accumulation of health stock and may also influence the decision to purchase health
insurance (Folland, Goodman and Stano, 2007), so in order to examine the effects of
insurance on health care consumption, controlling for these variables is necessary.
Differences between how subpopulations consume health care have also been found by
literature and will be examined (Levy and Meltzer, 2007). One such group, those with
chronic illnesses, will be addressed by controlling for chronic illness, since they
consistently consume more health care. These differences resulting from omitted
variable bias would skew the results because the changes in insurance policies would not
be responsible for all the variations of the health of individuals.
Endogeneity is another potential source of bias in the estimates. In this context,
those with poor health may decide to purchase more health insurance, knowing that they
will be consuming more health care in the future than those with better health,
confounding the correlation coefficient. It is expected that endogeneity would bias the
measured correlation between health insurance and health consumption so that there
seems to be a larger correlation than the true causal influence of health insurance on
health care consumption because individuals pick a plan which fits how they consume
health care. Endogeneity is hard to overcome in observational studies, but this problem is
partially addressed by controlling for income, education, and health status.
All regressions were run with all controls, without the income control, and
without both the income and health status controls to test the problems with the issue of
endogeneity. Health status and income controls were removed and the correlation
coefficients for each set of regressions are reported in each table. By removing layers of

controls one at a time, we can examine the degree of impact the removed control had on
the regression by comparing the two sets. If the values of the correlation coefficients or
marginal effects do not change significantly between regression sets, the removed control
had a small effect on the other variables, and therefore the insurance type has a large
effect on the variables.
The regressions were also run for the samples of the privately insured separately
to reveal the effects of different private insurance policies on the variables at hand. One
limitation of these regressions is that they may not be fully generalized to the population
because the measured sample may be skewed. Those who knew that they had private
insurance and what kind of private insurance they had were included in these regressions,
so individuals may have been excluded who have private insurance, but did not know
what kind. The fact that some individuals knew what kind of insurance they had and that
some did not, may reflect inherent differences between these two populations. It is
plausible that those who know what kind of insurance they have also know what sources
of care are less expensive to them and may consume care differently than the group who
does not know this information. Those who are able to label their own insurance type
represent a population with more information on the insurance market and therefore, by
examining this group alone, we are ignoring the element of the population with minimal
information on the insurance market. The number of individuals with private insurance,
but did not know what kind of private plan they had was 8,622, and 36,650 respondents
with private insurance did know their insurance type. One regression set was run
including those listing other private insurance, and another set was run with those with

other private insurance dropped from the data set. Both sets of private insurance
regressions were run relative to those with private HMOs or IPAs.
A. Statistical Analysis
Ordinary Least Squares (OLS) regressions were run for those variables which had
scalar values, such as frequency of doctor’s visits, ER visits, and hospitalizations. The
equation shows the relationship between variables for scalar and binary data sets, where
β0 - β9 = coefficients to be estimated, X = a vector of other confounding variables, and εi
= disturbance term.
[1] Y[scalar]* = Xβ0 + β1HMO + β2PPO + β3POS + β4FFS + β5OTHPRIV + β6SSP + β7MEDIC
+ β8GOV + β9NOINS + εi
With OLS regressions, the slope is equal to the correlation coefficient because the
variations between data points are constant. It is these correlation coefficients which are
compared in the analysis of the output data to determine the relationship between
specified variables.
A probit regression was run instead of an OLS regression for binary variables
because many of the assumptions made by the OLS regression are violated by this data
set. The main issue is the heteroscedasticity of the limited dependent variables. OLS
regressions assume a constant variance among variables and in this study the variables
have a range of variances, or are heteroscedastic. Since the variance is not constant and
predictions can fall outside of the [0,1] range, the probit regression classifies each
variable as a “1” or “0” if the prediction coefficient is above or below a certain threshold.
As the variance between data points and the regression line gets smaller, the slope

between the two points approaches the marginal effect. Dummy variables were created
for variables examined with a binary system, and probit regressions were run using
STATA for each type of insurance. This binary system was used for variables such as the
site for routine care, whether vaccines had been administered, and whether the patient
saw a nurse or physician’s assistant, general doctor, or specialist. Equation [2] shows the
relationship between variables for binary variables, where β0 - β9 = coefficients to be
estimated, X = a vector of other confounding variables, and εi = disturbance term.
[2] y* = Xβ0 + β1HMO + β2PPO + β3POS + β4FFS + β5OTHPRIV + β6SSP + β7MEDIC +
β8GOV + β9NOINS + εi y = 1 if y* > 0
y = 0 otherwise
The marginal effects are then a function of β’s and X’s which STATA calculates
and are shown as functions in the analyses. The value, y* is not observed and is often
referred to as a “latent” variable, and if this value is greater than zero, the observed y
value is defined as “1”. If we are examining whether or not an individual went to the ER,
y* would be defined as the desire and ability of a person to go to the ER. This level of
desire and ability cannot be directly observed, only the final outcome of whether or not
the person went to the ER.
Since the variance is irregular and predictions can fall outside of the [0,1] range,
we assume that var(εi) = 1 which means the scale of y* is fixed so that we can define the
probability of y = 1 in Equation [3] where, F = cumulative normal distribution function.

[3] P = Prob(y = 1) = Prob [εi > -(Xβ0 + β1HMO + β2PPO + β3POS + β4FFS +
β5OTHPRIV + β6SSP + β7MEDIC + β8GOV + β9NOINS)]
P = 1 – F[-(Xβ0 + β1HMO + β2PPO + β3POS + β4FFS + β5OTHPRIV + β6SSP +
β7MEDIC + β8GOV + β9NOINS)]
Probit regressions also include a variable which is the probability density function
for a standardized normal variable (Φ). It is important to include this correction factor to
determine accurate estimated correlation coefficients for prediction purposes because of
disproportionate sampling, or unequal numbers of observations in each group. This term
is added when examining how changes in the explanatory variables affect the
probabilities determined above. For a probit regression,
[4] ∂P/∂x = βΦ(Z)
where,
Z = β .
i = 1
With a probit regression, these derivatives are not constant, so they must be
calculated for each explanatory variable (Maddala and Lahiri, 2009). STATA calculates
these marginal effects and these values are displayed in the summary tables reported in
the appendices.
For the variable regarding the out of pocket amount of expenditures on health
care, an ordered probit regression was used. Since the dependant variable is multinomial,
or that different expenditures are reported as ranges, a normal probit or OLS regression

only reports on the average effect. The ordered probit model allows the marginal effects
going from one category to another to be non-linear. In other words, an ordered probit
allows the probability of ending up in each category to vary while an OLS regression
averages the effects of all the categories. Like in the probit model, there is a latent y*
variable which either exceeds or falls below a threshold, µ, but in this case, there is a
threshold value for each category. Each category represents a range of annual out of
pocket health care expenditures, where category 0 is zero dollars spent, category 1 is
0$499, category 2 is $500-$1,999, category 3 is $2,000-$2,999, category 4 is $3,000-
$4,999, and category 5 is over $5,000 spent. Here,
[5] y = n if µn-1 < y* < µn , where, n = 0, 1, 2, 3, 4, 5, or the desired category. The
same equation for the marginal effects as the probit model is used [2]. Since we want to
probe how changes in insurance, or the “predictor” variables, change the probability of an
individual falling into each category, we must find the probability of observing each
outcome. This is found by calculating the probability of finding y* between the two
threshold values, or,
[6] P(y = n) = P(µn-1 < y* < µn) , and since we established that y* = Xβ + εi , [7]
P(y = n) = P(µn-1 < Xβ + εi < µn) = P(µn-1 - Xβ < εi < µn - Xβ)
= Φ(µn-1 – Xβ) – Φ(µn – Xβ) ,
where Φ is the probability density function for a standardized normal variable as seen in
equation [4] (Jackman, 2000).

Chi-squared tests will be run on all regression sets to determine statistically
significant differences between insurance types. A 95 percent confidence interval will be
used to determine statistical significance. The marginal effects of the regressions are
summarized in Appendix 3 with all insurance types, and a complete example of a set of
the marginal effects with all controls can be found in Appendix 4.
VI. Discussion
The findings derived from analysis of the correlation coefficients, marginal effects
and chi square tests are broken down into sections based on their implications. First,
access and affordability of care will be discussed, followed by an analysis on the
utilization of types of health care. The type of health professional seen was also
examined and will be discussed in relation to expensive versus inexpensive care
consumption by patients. The findings regarding the usual location of health care
consumption have major efficiency, or inefficiency, implications and are presented in
regards to which plans encourage efficient or inefficient consumption of care. The
location of care consumption is of great consequence because it highlights severe
inefficiencies in insurance plans if they encourage individuals to consume care routinely
at an ER or free clinic.
A. Affordability of Care and Preventative Care Analysis
The overall out of pocket spending for individuals was examined and variations in
these expenditures were found between insurance types. Individuals with Medicaid plans
were 10.7 and 7.1 percent more likely to spend zero or less than $500 out of pocket

respectively than other plans. Those with other government insurance and military
insurance also followed this trend of being more likely to have spent between zero and
$500 on health care out of pocket in the past year. The marginal effects broken down for
each range of expenditures are reported in Table 1 seen in Appendix 3. These ranges are
raw out of pocket expenditures and are not corrected in any way for the income of the
individual. Only the amount spent on health care is assessed by this analysis, and the
affordability of care is another issue which is examined next.
Table 2 shows that all types of insurance were less likely to both delay care
because of cost and to not get needed care because of cost than the uninsured. This result
was expected, but using a chi-squared test, it was found that those individuals with
private insurance are less likely than those on Medicare and with other government
insurance to delay care because of cost, are less likely than those on Medicare, Medicaid,
and other government insurance to neglect to get needed care because of cost. Likewise,
all forms of insurance were less likely to not be able to afford prescription drugs than the
uninsured, and those with private insurance were the least likely to not be able to afford
prescription drugs for all types of insurance except military insurance.
The variation seen between regression sets with and without health status and
income is consistent with the expected effects of health status and income on the
specified variables. The trends indicate that the coefficients without health status and
income are less negative than those regressions which control for these factors. These
trends are consistent with the literature in that as health status and incomes rise, people
would be less likely to delay or neglect needed care because of cost or not be able to

afford prescriptions because if they are in excellent health, care is not needed and if they
have a high income, affordability of care is not a problem. It has also been shown that
both health status and income are positively correlated with selection into a health
insurance policy in general. It follows that as health status increases and incomes rise,
individuals may have increased access to insurance because insurance companies want to
insure them, and also are more likely to get plans with greater coverage because of
employment. Once these effects which skew the regressions in the positive direction are
accounted for, the coefficient becomes more negative (Table 2).
Within the private insurance group, those with other private insurance and PPO or
POS plans had statistically significant positive marginal effects on the probability of
delaying care because of cost relative to those with HMOs or IPAs. This demonstrates
that those with HMOs or IPAs have a lower incidence of delaying medical care due to
cost. This trend continues with not obtaining needed care because of cost. Those with
other private insurance and PPO or POS plans are more likely to not obtain needed care
because of cost than those with HMO or IPA plans. Also, of the privately insured, those
with other private insurance were the most likely to say that they cannot afford
prescription drugs at a statistically significant level (Table 8). This finding is interesting
because it illustrates the trends discussed by the literature which state that HMOs cause
people to have increased utilization of preventative care with fewer barriers to this cheap
care. It does not address the idea of HMOs limiting more expensive care via gatekeepers
and capitation policies.

To examine the provision of basic preventative care, regressions were run for
whether individuals received pneumonia and Hepatitis B vaccines. Having insurance
increased the probability of getting a vaccine with the most likely people to get the
vaccine being those with Medicare and military insurance for both vaccines (Table 3).
Little information could be derived from the regressions concerning only private
insurance for vaccinations, but it was found that those with PPO or POS plans were less
likely to have been vaccinated for pneumonia than those with other private insurance at
the 0.05 significance level.
B. Frequency and Instance of Utilization of Health Care Analysis To
examine the utilization of care, both the frequency and instance of different types of care
were analyzed. The instance and frequency of overnight hospitalizations and surgery, and
the frequency of ER visits and doctor’s visits regressions can be found in Tables 4 and 5.
It was found that those with private insurance, other government insurance, and military
insurance have a lower incidence of reporting at least one overnight hospitalization than
those with Medicare and Medicaid, with those with all types of insurance being more
likely to spend a night in a hospital than the uninsured. In terms of frequency of
overnight hospitalizations, there was a positive correlation for all types of insurance,
except for private insurance without controlling for income or health status, but this value
was not statistically significant at the 0.05 level. Those with private and military
insurance had the lowest correlation coefficient and have a lower frequency of overnight
hospitalizations than all other insurance types, except other government insurance (Table
4). Among the privately insured, those with FFS plans were more likely to both list that

they were hospitalized, and have the highest frequency of hospitalizations than those with
HMOs/IPAs, PPOs/POSs, or other private insurance at a statistically significant level
when the controls of income and health status were removed (Table 10). This result of
the FFS policies having the highest frequency of hospital visits is also consistent with the
findings of regressions run without those listing other private insurance at a statistically
significant level (Table 16).
There is also a positive correlation between having at least one surgery and
having some type of insurance, and chi-square tests indicate that those with private
insurance have less surgery than those with Medicaid at a statistically significant level.
The frequency of surgical procedures follows the same trend, with statistically significant
positive correlation coefficients for all insurance types. Those with Medicare and
Medicaid are more likely to have a higher frequency of surgical procedures at a
statistically significant level than those who are privately insured (Table 4). When types
of private insurance were examined separately, it was found that those with FFS plans
were the least likely to have had surgery and also have a lower frequency of surgery than
all other private insurance types at a 0.05 significance level. This result was surprising
because those with FFS plans have a higher incidence and frequency of overnight
hospitalizations than all other plans, but have a lower incidence and frequency of surgery
(Table 10). Those with FFS plans are hospitalized overnight more frequently than others,
but do not require surgery for these hospitalizations, therefore the cost of each
hospitalization may not be as high as some other plans. Hospitalizations for diabetes,
bronchitis, pneumonia, some cancers, flu, and infectious diseases typically do not result

in surgery, so those with FFS plans may be hospitalized for these types of conditions and
therefore require less surgery. The frequency of hospitalization is a good indicator of
health care use, but it does not tell us what type of health care was consumed at each
hospitalization so we can derive no direct information from the data about cost per
hospitalization. This limits the analysis of efficiency implications, but it is possible that
high levels of hospitalizations and low frequency of surgery indicates an excessive use of
overnight observational stays.
An example of possible overuse of overnight hospitalizations is the stay of
patients in the Intensive Care Unit, ICU, after gastric bypass surgery. The ICU is a more
expensive location in the hospital to be kept overnight because of the increased level of
supervision by nurses and doctors as well as the more advanced technology utilized to
monitor the patient. The movement of patients to the surgical floor is the goal of doctors
and hospitals because it is less costly to the hospitals to monitor the patient and indicates
positive outcomes of a procedure because the patient must be doing well to move them to
the surgical floor. It was found by Grover et al (2010) that the common post-operative
stay of gastric bypass patients with obstructive sleep apnea in the ICU is an unnecessary
precaution. Typically, gastric bypass patients with obstructive sleep apnea are kept in the
ICU overnight to allow for close observation to avoid pulmonary complications, but it
was found that there were no difference in the length of overall hospital stay or major
complications between group kept overnight in the ICU and the group moved directly to
the surgical floor. This indicates that the use of ICU beds for these gastric bypass patients
with obstructive sleep apnea is an inefficient allocation of an expensive resource because

the marginal benefits of keeping the patient in the ICU are very small. This inefficient
length of expensive care is one major issue with the system, but the location of care can
also yield inefficiency.
As previously discussed, the ER is an inefficient location to consume health care
because of the high financial burden it places on hospitals. Keeping an ER heavily
staffed around the clock is a massive drain on a hospital and ER use must be examined
when searching for inefficiency. It was found that the frequency of ER visits varies
significantly between insurance types. All insurance types except the privately insured
have a positive correlation coefficient for frequency of ER visits. This negative
coefficient is not significant at the 0.05 level, except when income and health status are
not controlled for, but it can be said with statistical significance that the privately insured
frequent the ER less often than those with Medicare, Medicaid and other government
insurance (Table 5). This finding is interesting because the ER is an inefficient location
of health care consumption due to high costs incurred by the hospital. It is expected that
the uninsured would frequent the ER to a large extent because they would receive care
regardless of their ability to pay. It is surprising that some insurance plans encourage
individuals to frequent the ER more often than the uninsured, as represented by the
positive correlation coefficient. This result could be the result of public plans such as
Medicare not covering regular checkups. To minimize the cost to the individual, a person
would go to the ER for routine care because it would cost less than making a doctor’s
appointment. Also, even if a doctor’s appointment is covered by Medicaid many
physicians do not accept or limit Medicaid patients because the reimbursement rate is

lower than for those with private plans. In this light, it is possible that increasing
reimbursement to physicians and covering routine care by Medicaid and Medicare may
reduce overall costs. Inducing individuals not to utilize the ER as often would yield a net
savings for the system if they instead consumed care at a more efficient location and
level. Plans which encourage an increased frequency of ER visits should be reexamined
to eliminate this inefficient consumption of health care.
When the privately insured were examined alone, there was not found to be any
statistically significant difference in ER utilization between insurance types. It would be
expected that since the privately insured had the lowest frequency of ER visits, that this
would be compensated for by an increase in the frequency of doctor’s visits relative to all
other types of insurance, but this is not the case. It was found that all types of insurance
had a positive relationship with frequency of doctor’s visits, but those with private
insurance had a lower frequency of doctor’s visits than all other insurance types except
other government insurance at a statistically significant level. Those with Medicaid had
the highest correlation coefficient relative to all other types of insurance, meaning that
they have the highest frequency of doctor’s visits (Table 5). Those with Medicaid
insurance plans were also the most likely to have had ten or more doctor’s visits in the
past year at a statistically significant level (Table 5). Since health status, ambulatory care
conditions, and chronic conditions are controlled for in that regression set, it follows that
those with Medicare plans are consuming care inefficiently in the form of excessive
doctor’s visits. This illustrates the imperfect capturing of true health by the controls of
health status, ambulatory care conditions, and chronic conditions. The true health status

is controlled for as much as possible with the data set at hand because of availability of
data. Including other health controls would severely limit the sample size and could lead
to inaccurate sample populations.
Among the privately insured, those with PPO plans frequent the doctor’s office
more than those with HMO or other private insurance plans at a statistically significant
level (Table 11). It was also found that when the other private insurance group is
dropped from the sample, PPO plan individuals frequent the doctor more often than those
with HMOs (Table 17). Those with PPO plans were also more likely than those with
HMO plans to list having ten or more doctor’s visits in the past year. This trend
continues in regressions which control for health status and in those which do not control
for health status. This implies that with the effects of health status removed, PPO
enrollees are consuming more care in the form of doctor’s visits than other private
insurance types (Table 11).
All regressions including health status were run with an ambulatory care sensitive
condition indicator variable as a control, but the coefficients of these variables are also
included in Tables 5, 11, and 17. This ambulatory care sensitive condition variable may
reveal how insurers and patients select for health insurance. Those plans with
probabilities of ambulatory care conditions may exhibit endogeneity, meaning that
individuals may have selected specific plans because of their health status and conditions
before they acquired these plans. Causality is difficult to determine but it is important to
discuss that self selection or insurer selection may have resulted in those with ambulatory
care sensitive conditions having these plans. Therefore, it is possible that these

conditions are not the result of the plans, but instead that the plan chosen by an individual
is the result of their underlying health status. The health status of the individual was
controlled for by including self reported health status, ambulatory care conditions, stroke,
and chronic conditions such as cancer. Although all of these factors were controlled for,
they do not assess the complete picture of the health of the individual. It is these omitted
health controls which contribute to the underlying health status which may be skewing
coefficients and causing endogeneity.
C. Type of Health Care Consumption Analysis
The type of health care professional seen - nurse or physician’s assistant, general
MD, or specialist - was also examined. It was found that there were positive correlations
between all insurance types and seeing all health care professional types relative to the
uninsured, as expected. When asked if a nurse or physician’s assistant (PA) was seen,
those with military insurance had the highest measured impact at a statistically significant
level. It was also found that those with Medicare plans were the least likely of all
insurance types to have seen a general MD. Also, the privately insured reported seeing a
general MD less than those with Medicaid and other government insurance. For
specialist visits, all types of insurance had positive correlation coefficients, but they were
not found to be different at a statistically significant level (Table 6).
When private insurance was examined alone, it was found that those with FFS
plans were the least likely to have seen a general MD in regressions with and without
health status and insurance controls. It was also found that there were no statistically
significant differences among private insurance types for whether they had seen a nurse

or physician’s assistant. Those with PPO or POS plans were more likely to have seen a
specialist than those with other private insurance or HMO plans (Table 12).
D. Location of Health Care Consumption Analysis
The marginal effects between groups with and without health status and income
controls are very similar for those who listed the usual location of health care
consumption as the ER. This means that the insurance type has a large impact on the
outcome of whether an individual utilizes the ER as their usual location of health care.
Those with private insurance are less likely to have the ER as their usual location of care
than all other types of insurance at a statistically significant level. This finding is
interesting, because it is inefficient to consume care at the ER, and these individuals are
not only consuming care there, but listing the ER as their usual location of health care
consumption; this is very inefficient. There was little difference among the privately
insured groups concerning whether the usual location of care is the ER, with very low
marginal effect values for each private insurance type (Table 13).
Those with private insurance are also the least likely to list their usual location of
health care consumption as a free clinic at a statistically significant level. This result was
expected, but the degree of the differences is very large. Individuals with private
insurance were between 11 and 12 percentage points less likely than the uninsured to list
a free clinic as the usual source of care, whereas military and other government insurance
were between 12 percentage points and 10 percentage points more likely than the
uninsured. Free clinics are also very inefficient locations to receive health care because
they are a financial drain on health care providers. These very strong numbers indicate

that other government and military insurance plans contain some inherent motivation for
individuals to consume care inefficiently (Table 7). Within the privately insured groups,
those with other private insurance were the most likely to list their usual location of care
as a free clinic at the 0.05 significance level (Table 13).
For those with other government and military insurance, the marginal effects were
statistically significant and negative, indicating that they are less likely to list the usual
location of care listed as the office. These two insurance types are the least likely to list a
doctor’s office as the usual location of care than all other insurance types. The most
likely to list the doctor’s office as the usual location of care was the privately insured
across all regression sets (Table 7). Among the privately insured, individuals with other
private insurance were the least likely to report a doctor’s office as the usual location of
care (Table 13). Those with private insurance are also the least likely to list an outpatient
clinic as their usual location of care than all other types of insurance at a statistically
significant level. The insurance group that were the most likely to list an outpatient clinic
as the usual location of health care consumption were those with military insurance
policies. This could be due to the structure of the veteran’s hospitals and an emphasis on
outpatient care (Table 7). There was little difference between the private insurance types
for the outpatient clinic variable, implying that no one private plan encourages or
discourages outpatient clinic use than another private plan in this study (Table 13).

VII. Conclusion
Efficiency analysis of various insurance policies is imperative when determining
which methods of insurance provision should be expanded or reduced to help slow
increasing health care costs. A high degree of ER utilization is an indicator of inefficient
consumption of health care. Since it was found that the privately insured frequent the ER
less than Medicare and Medicaid, some aspect of Medicare and Medicaid is inducing
individuals to consume more ER visits. These incentives are important to identify so we
can include them in an ideal insurance system. It was also found that there were
statistically significant positive correlations between the frequency of ER visits and
individuals on Medicare, Medicaid, other government insurance, and military insurance,
relative to the uninsured. This illustrates major flaws in the system. It would be expected
that the uninsured would consume the most ER visits because the ER is a location with
guaranteed access to quality health care, but these results indicate that some insurance
plans induce individuals to consume more ER visits than the uninsured. These results are
consistent with the findings of Zuckerman and Shen (2004) who observed that public
insurance plans, such as Medicare and Medicaid, were 2.08 times more likely to be
frequent users of the ER, the highest correlation coefficient of all insurance types.
The increased utilization of the ER by individuals on Medicare and Medicaid
could be due to the characteristics of the policies which limit how enrollees can consume
care. Medicare does not cover doctor’s visits for routine care. This means that it is
cheapest for the individual to go to the ER or a free clinic for routine care than it would
be to consume care efficiently at a doctor’s office. This incentive could explain the

findings in this paper and should be addressed in health care reform. This unexpectedly
high utilization of the ER by Medicaid enrollees could be due to the low reimbursement
rates by Medicaid for routine doctor’s visits. 21.0 percent of doctors do not accept
Medicaid enrollees as new patients because the reimbursement rates are so low, and this
figure rises to 24.7 percent with states with delays in reimbursement, magnifying the
problem (Cunningham and O’Malley, 2009). The low Medicaid participation rate of
physicians forces people to consume care at other locations, such as the ER. The fact that
doctors are not accepting Medicaid amplifies the issues with access to health care. Those
on Medicaid have low incomes or disabilities by definition, so any decrease in access
disproportionately disadvantages this group of individuals. The equity issue then presents
itself again; by providing low income individuals with insurance which does not
maximize access to care, we are limiting the benefits this insurance can have. Low
reimbursement rates also may cause hospitals and doctors to induce the demand of health
care by ordering more tests, as previously explained. It may seem counterintuitive
initially, but if the idea of supplier induced demand is true, it may lower the net costs of
the system if Medicare covered routine doctor’s visits and Medicaid reimbursement rates
were elevated because it would decrease incentives for the provision of unnecessary care.
Overcrowding of ERs and low Medicaid reimbursement rates for treatment
provided by the ER, has put financial stress on many hospitals causing them to close ERs
(Steele et al, 2008). In Califonia, ER closures have taken a significant toll on hospitals.
Since 1998 in Los Angeles County alone, 40 ERs have closed while only one has opened
(Los Angeles Times, 2007). Medi-Cal, the Californian Medicaid service, has one of the

lowest reimbursement rates and hospital administrators shave been forced to close the
doors of their ERs in order to keep the whole hospital from going bankrupt. This issue is
not contained in California; nationally, ER utilization has increased by 26 percent, while
the numbers of ERs has decreased by 9 percent in the past decade (Kellerman, 2006).
Each time an ER closes, the geographic area they serve faces an access to health care
issue. Because the reason the ERs are closing is that the ER is not getting reimbursed for
the care they provide, the people who are getting displaced by this closure generally have
low incomes. Reducing health care access for a population which is ill-equipped to
compensate for this change because they have minimal resources to gain access to quality
care, illustrates an equity issue. Closing ERs and threatening to close entire hospitals has
many negative social welfare implications, the most direct of which is the lack of access
to health care. As ERs close, the burden of patients then gets shifted to another, already
stressed ER. Moving patients around from overcrowded ER to overcrowded ER could
compromise patient care and lead to poor health outcomes.
Another interesting finding which merits more investigation is that FFS enrollees
consume more overnight hospitalizations, but fewer surgeries than all other types of
private insurance. Individuals with FFS plans may be hospitalized more frequently for
conditions that do not require surgery such as diabetes, bronchitis, pneumonia, some
cancers, flu, and infectious diseases. Although the frequency of hospitalization is a good
indicator of health care use; it does not tell us what type of health care was consumed at
each hospitalization. This lack of data limits the ability to determine if this pattern of
consumption is efficient because we do not have information about cost per

hospitalization. It is both possible that high levels of hospitalizations and low frequency
of surgery indicates an excessive use of overnight observational stays, or that other types
of insurance are over-consuming surgeries whereas FFS patients do not. Further research
is required to determine efficiency implications of this consumption pattern among FFS
enrollees.
The inefficiencies discussed here have many different origins which should be
examined further. Identifying and quantifying the flaws in the system is a first step; now
we must find the root of these errors and correct them in order to improve health care
provision and consumption. The finding that Medicare and Medicaid patients consume
abnormally high levels ER visits is astoundingly pertinent to the recent addition of more
individuals to Medicaid. The recently signed health care reform law adds more
individuals to Medicaid and private insurance by expanding Medicaid qualifications and
mandating health insurance. Adding more people to plans which induce inefficient health
care consumption will only magnify the current issue of rising health care cost when
these reforms were intended to reduce costs. The current reforms also raise Medicaid
reimbursement rates, but whether these rates were increased enough to remedy the
inefficiencies induced by these low rates is yet to be determined. The Massachusetts
reforms provide an example for current health reforms and a warning against the same
pit-falls which have caused health care costs in Massachusetts to rise above their
expected values. More research is necessitated on this topic before we can hone in on the
most efficient and applicable insurance policies for the United States, but it merits

attention because without this understanding, it would be difficult to solve the problems
in the health care system we face today.

