



The Market for Health-Care Services
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
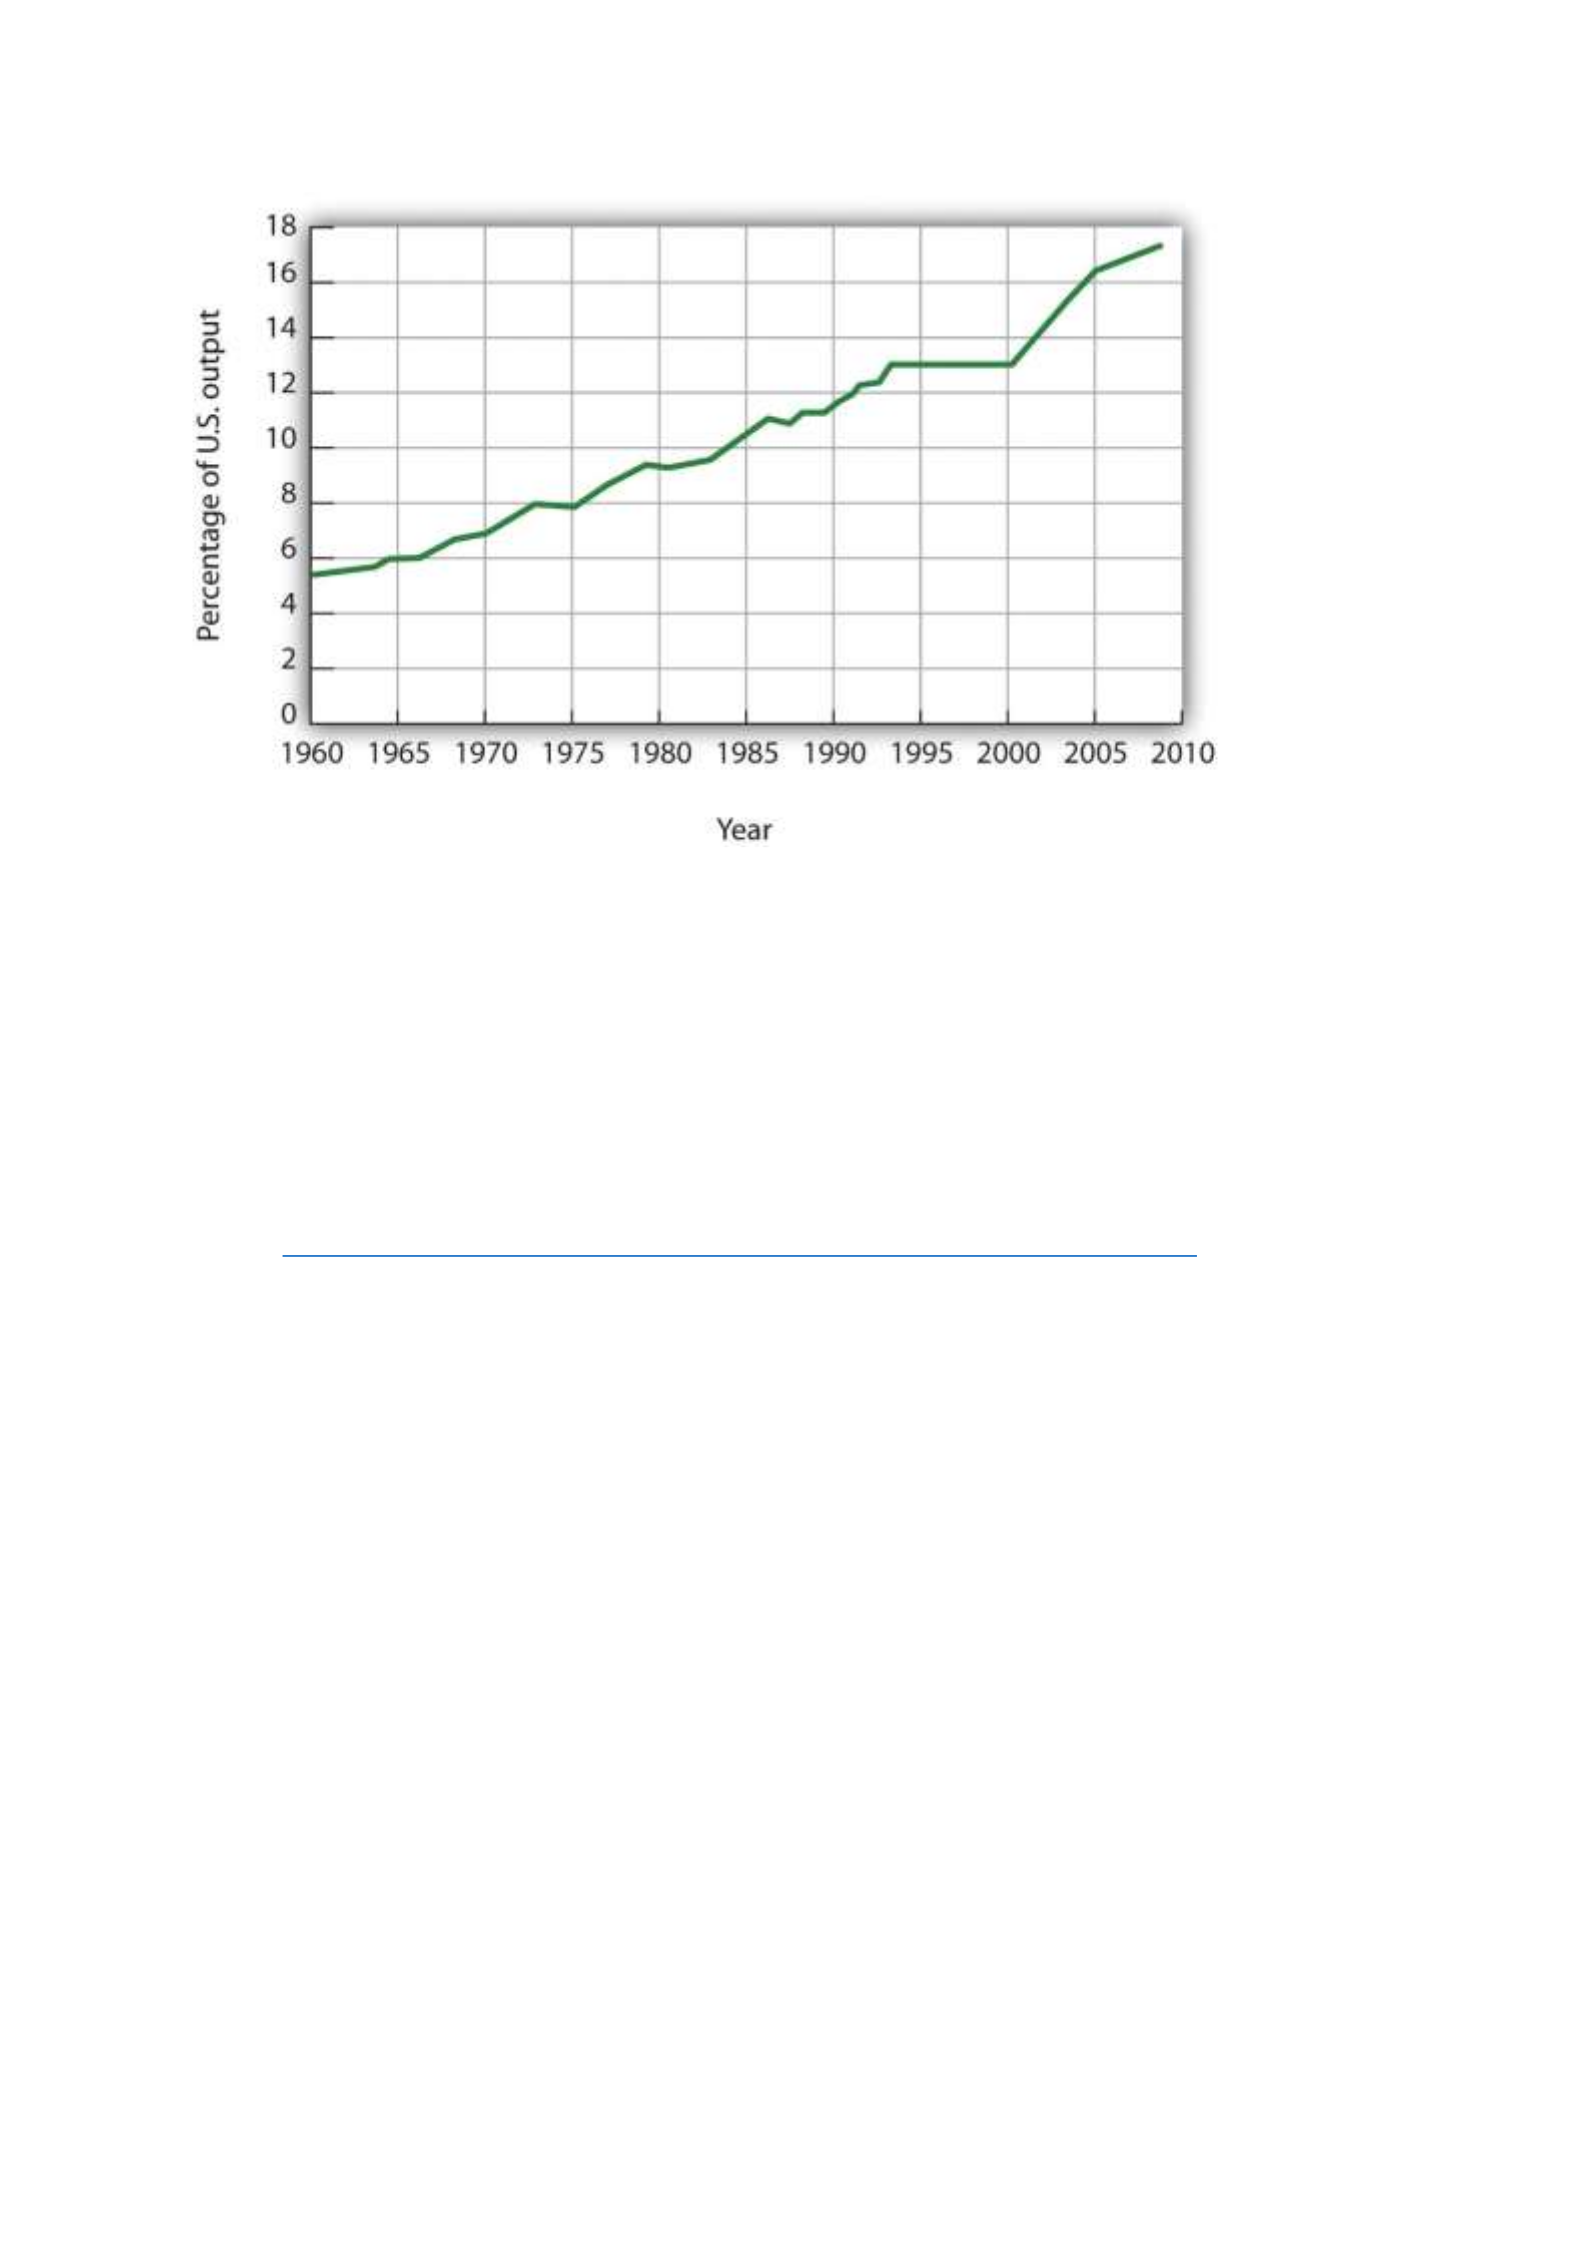
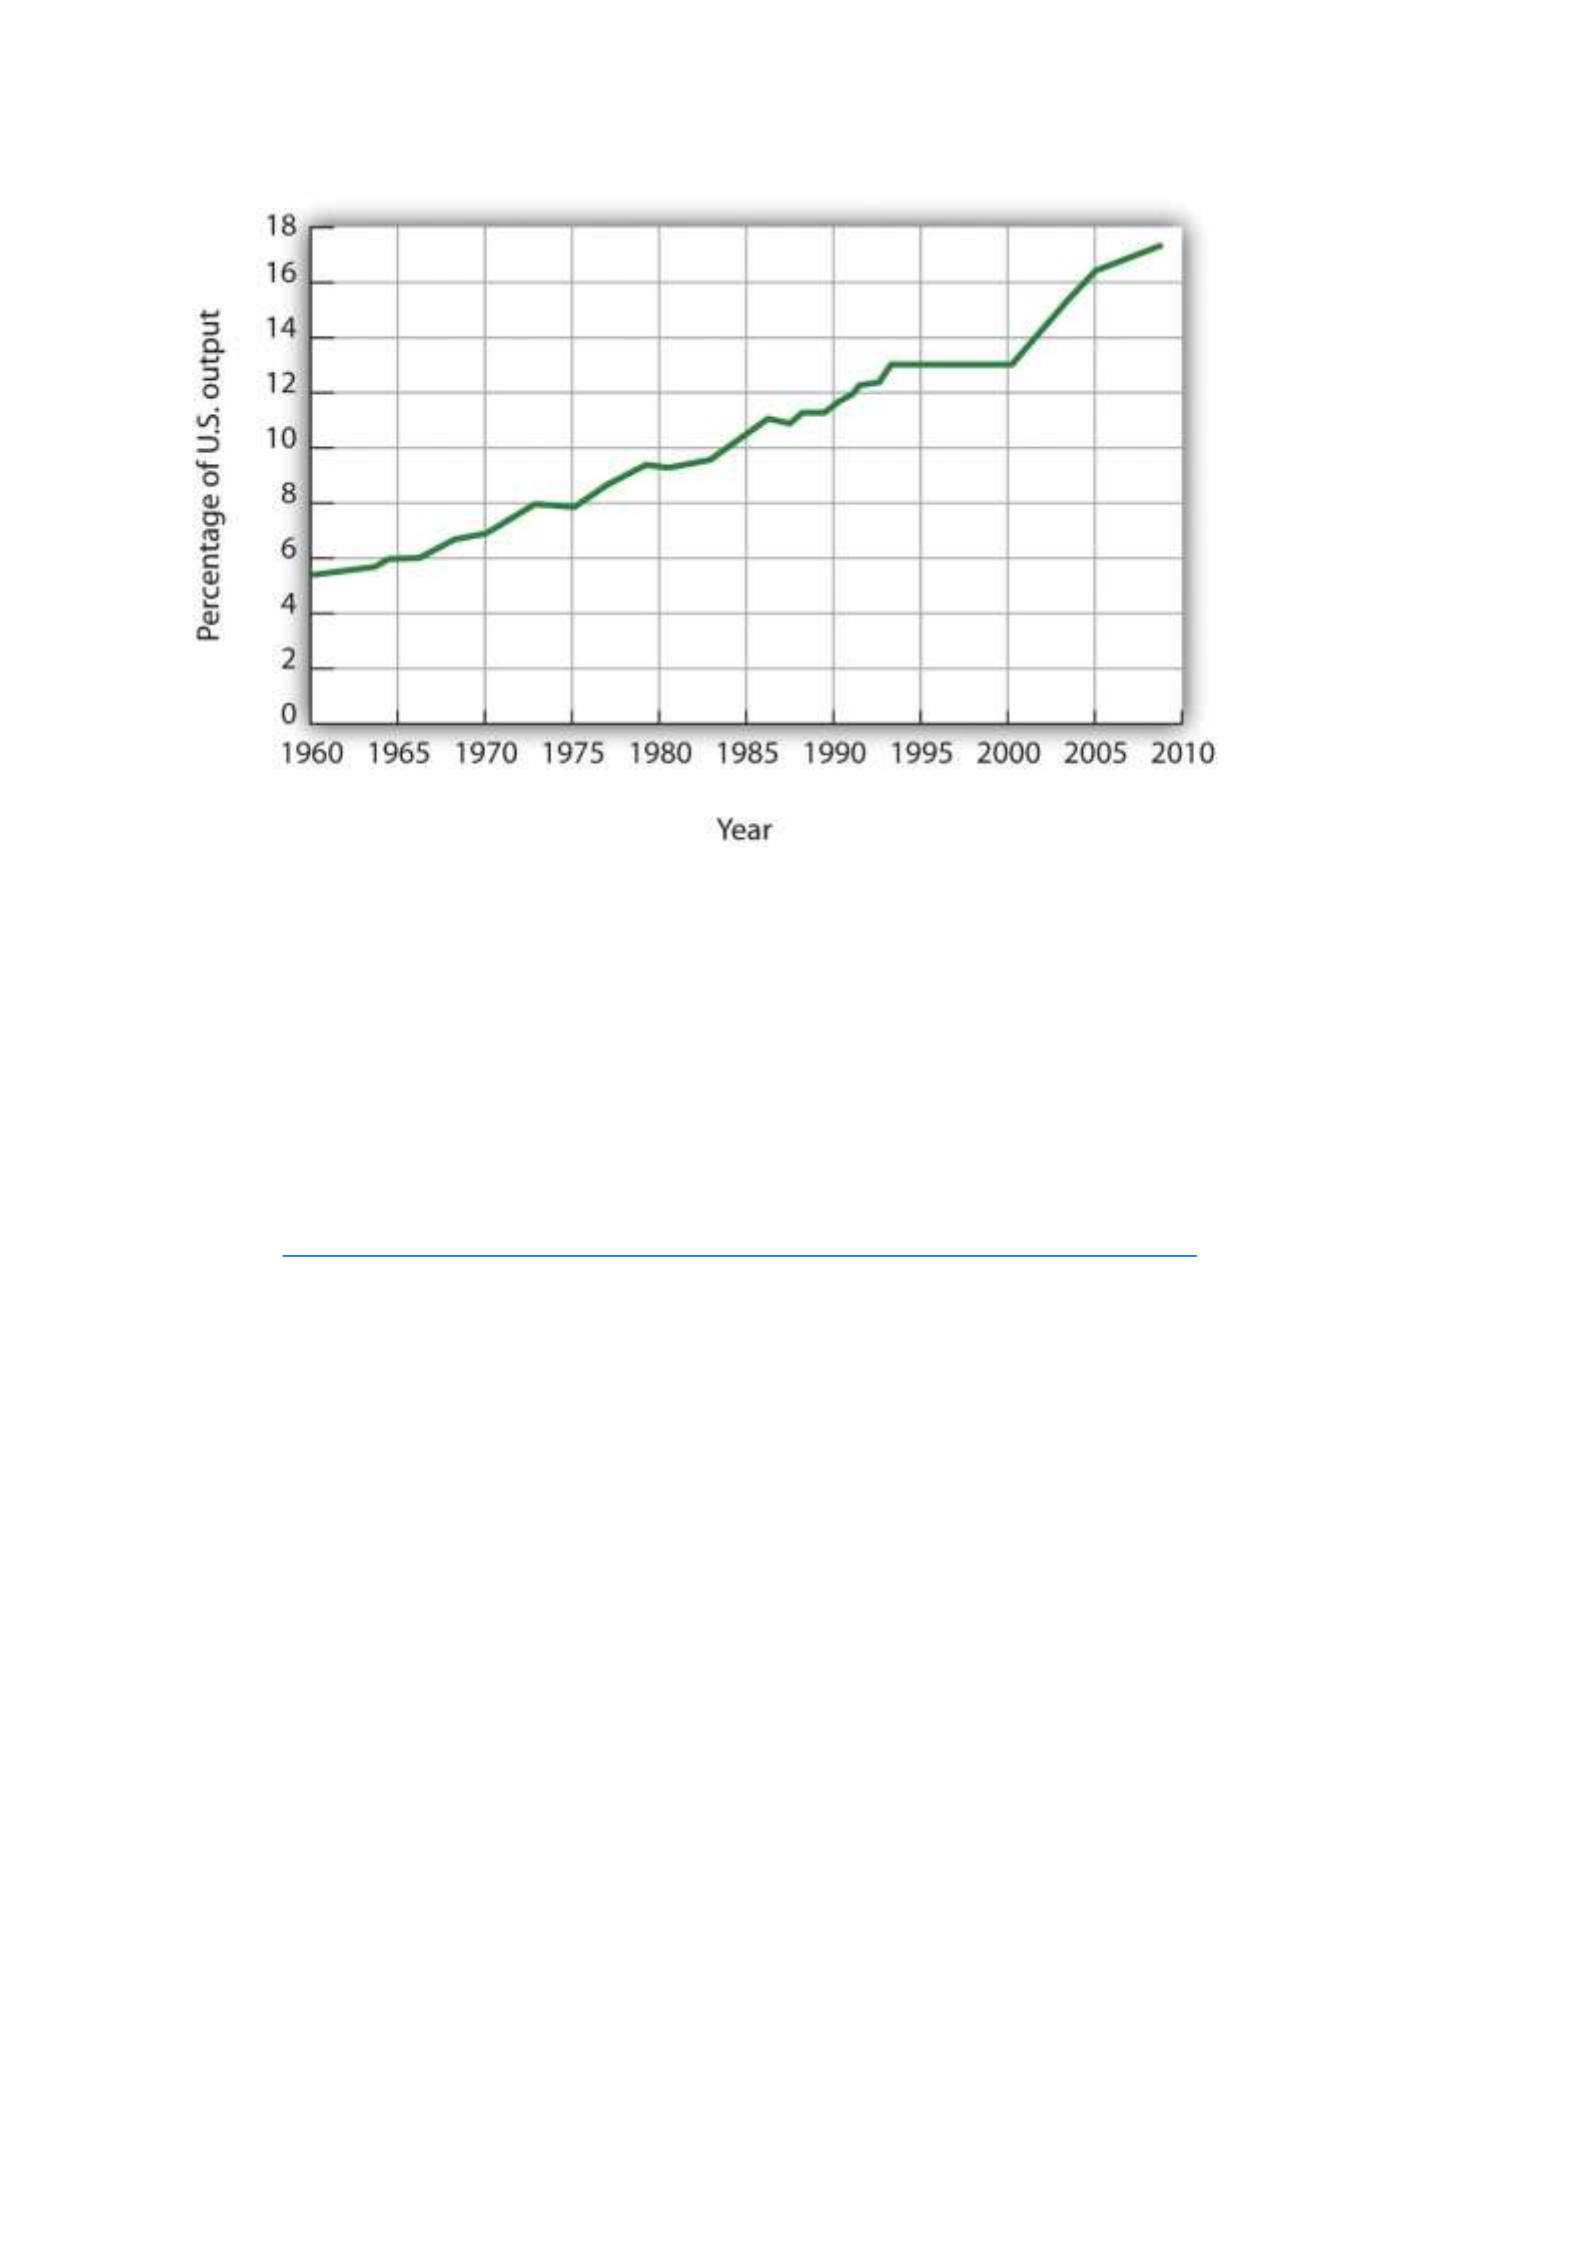
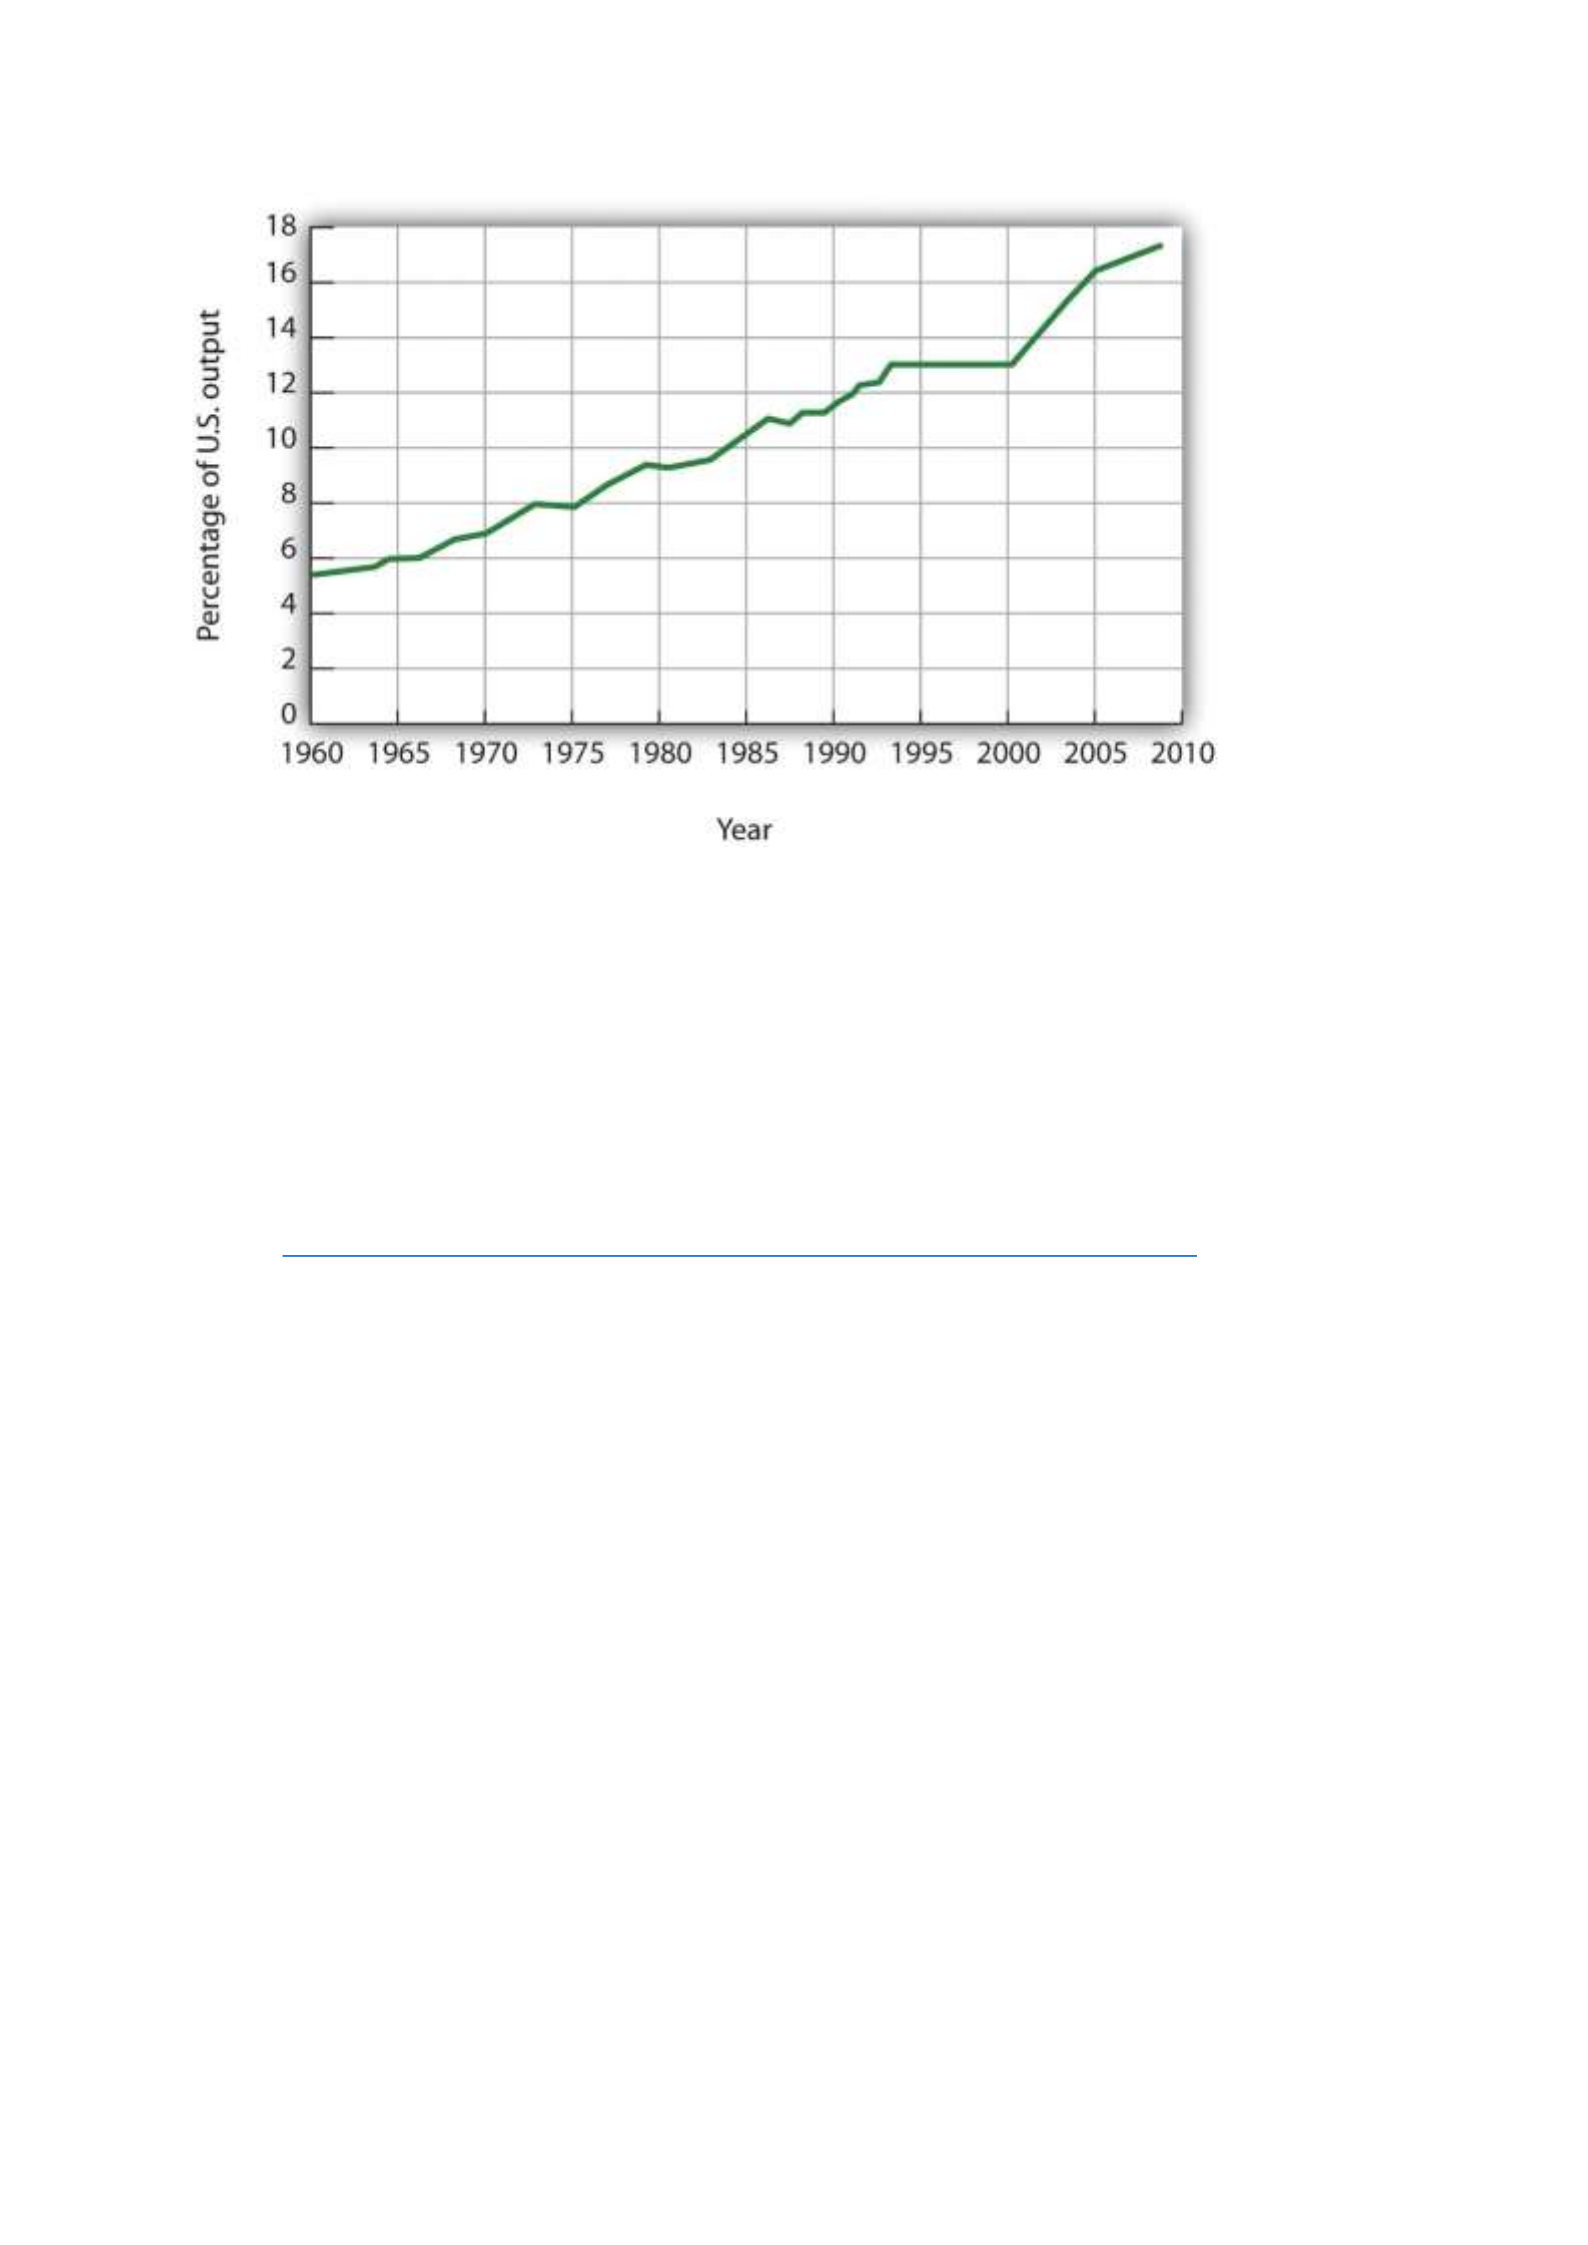
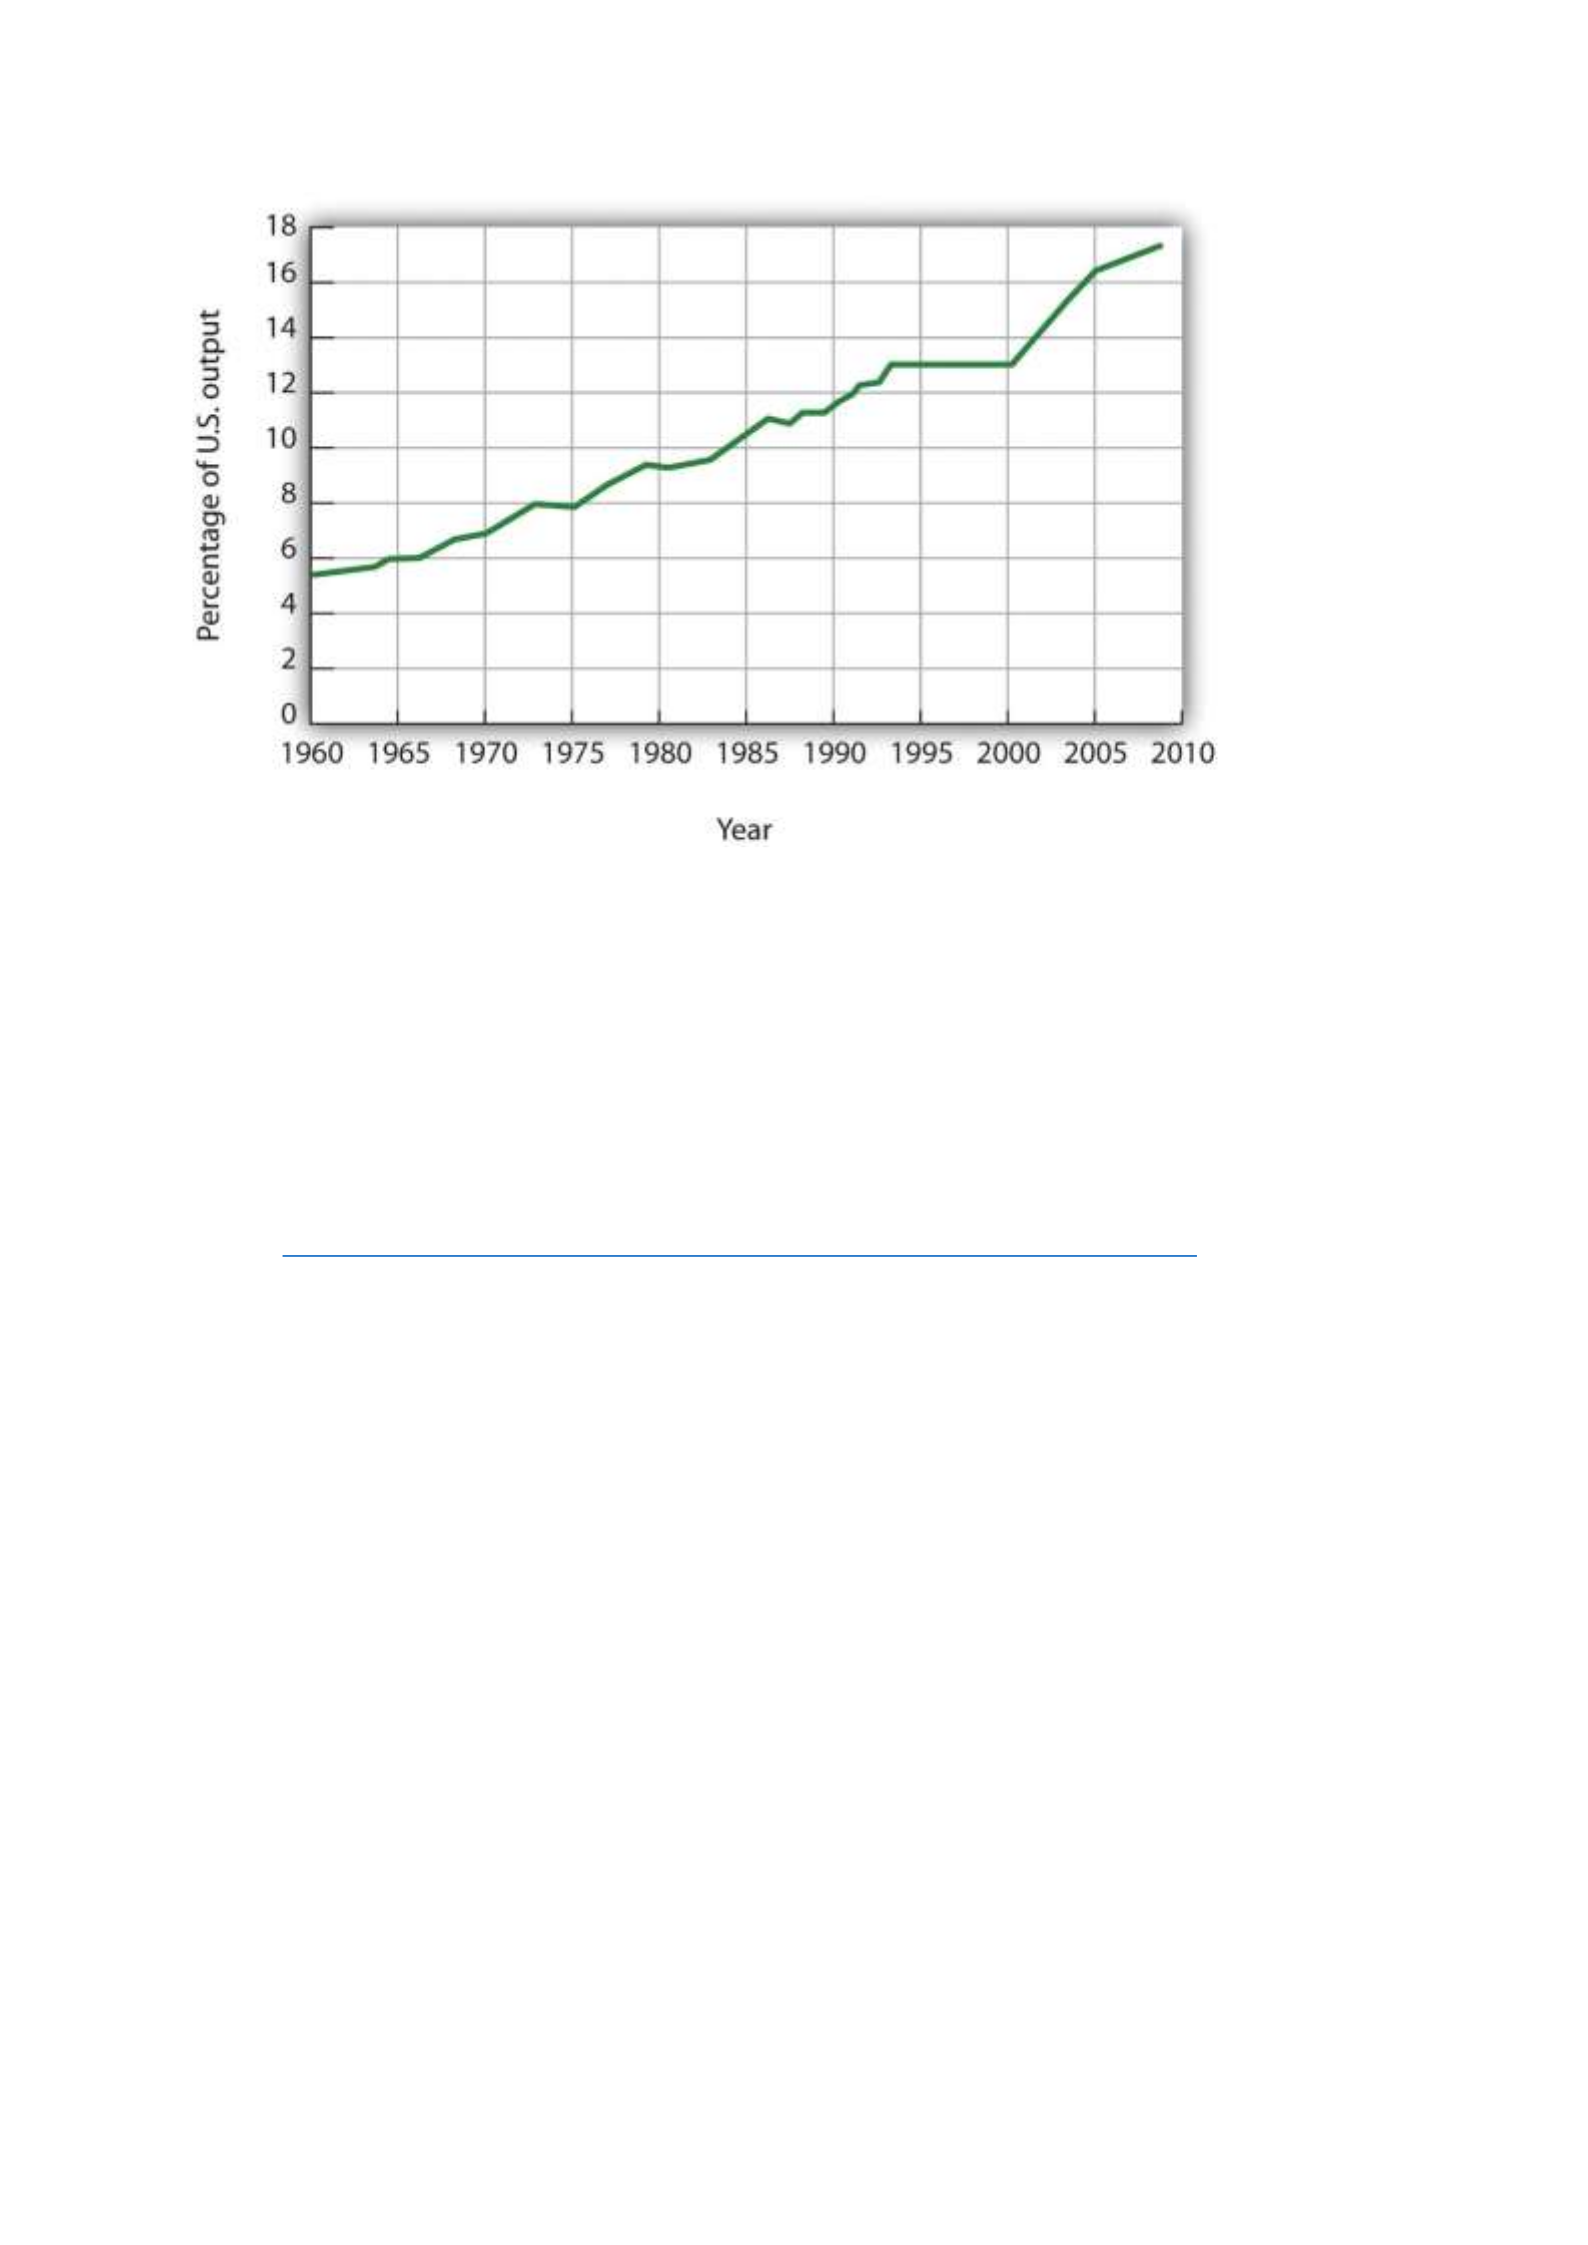
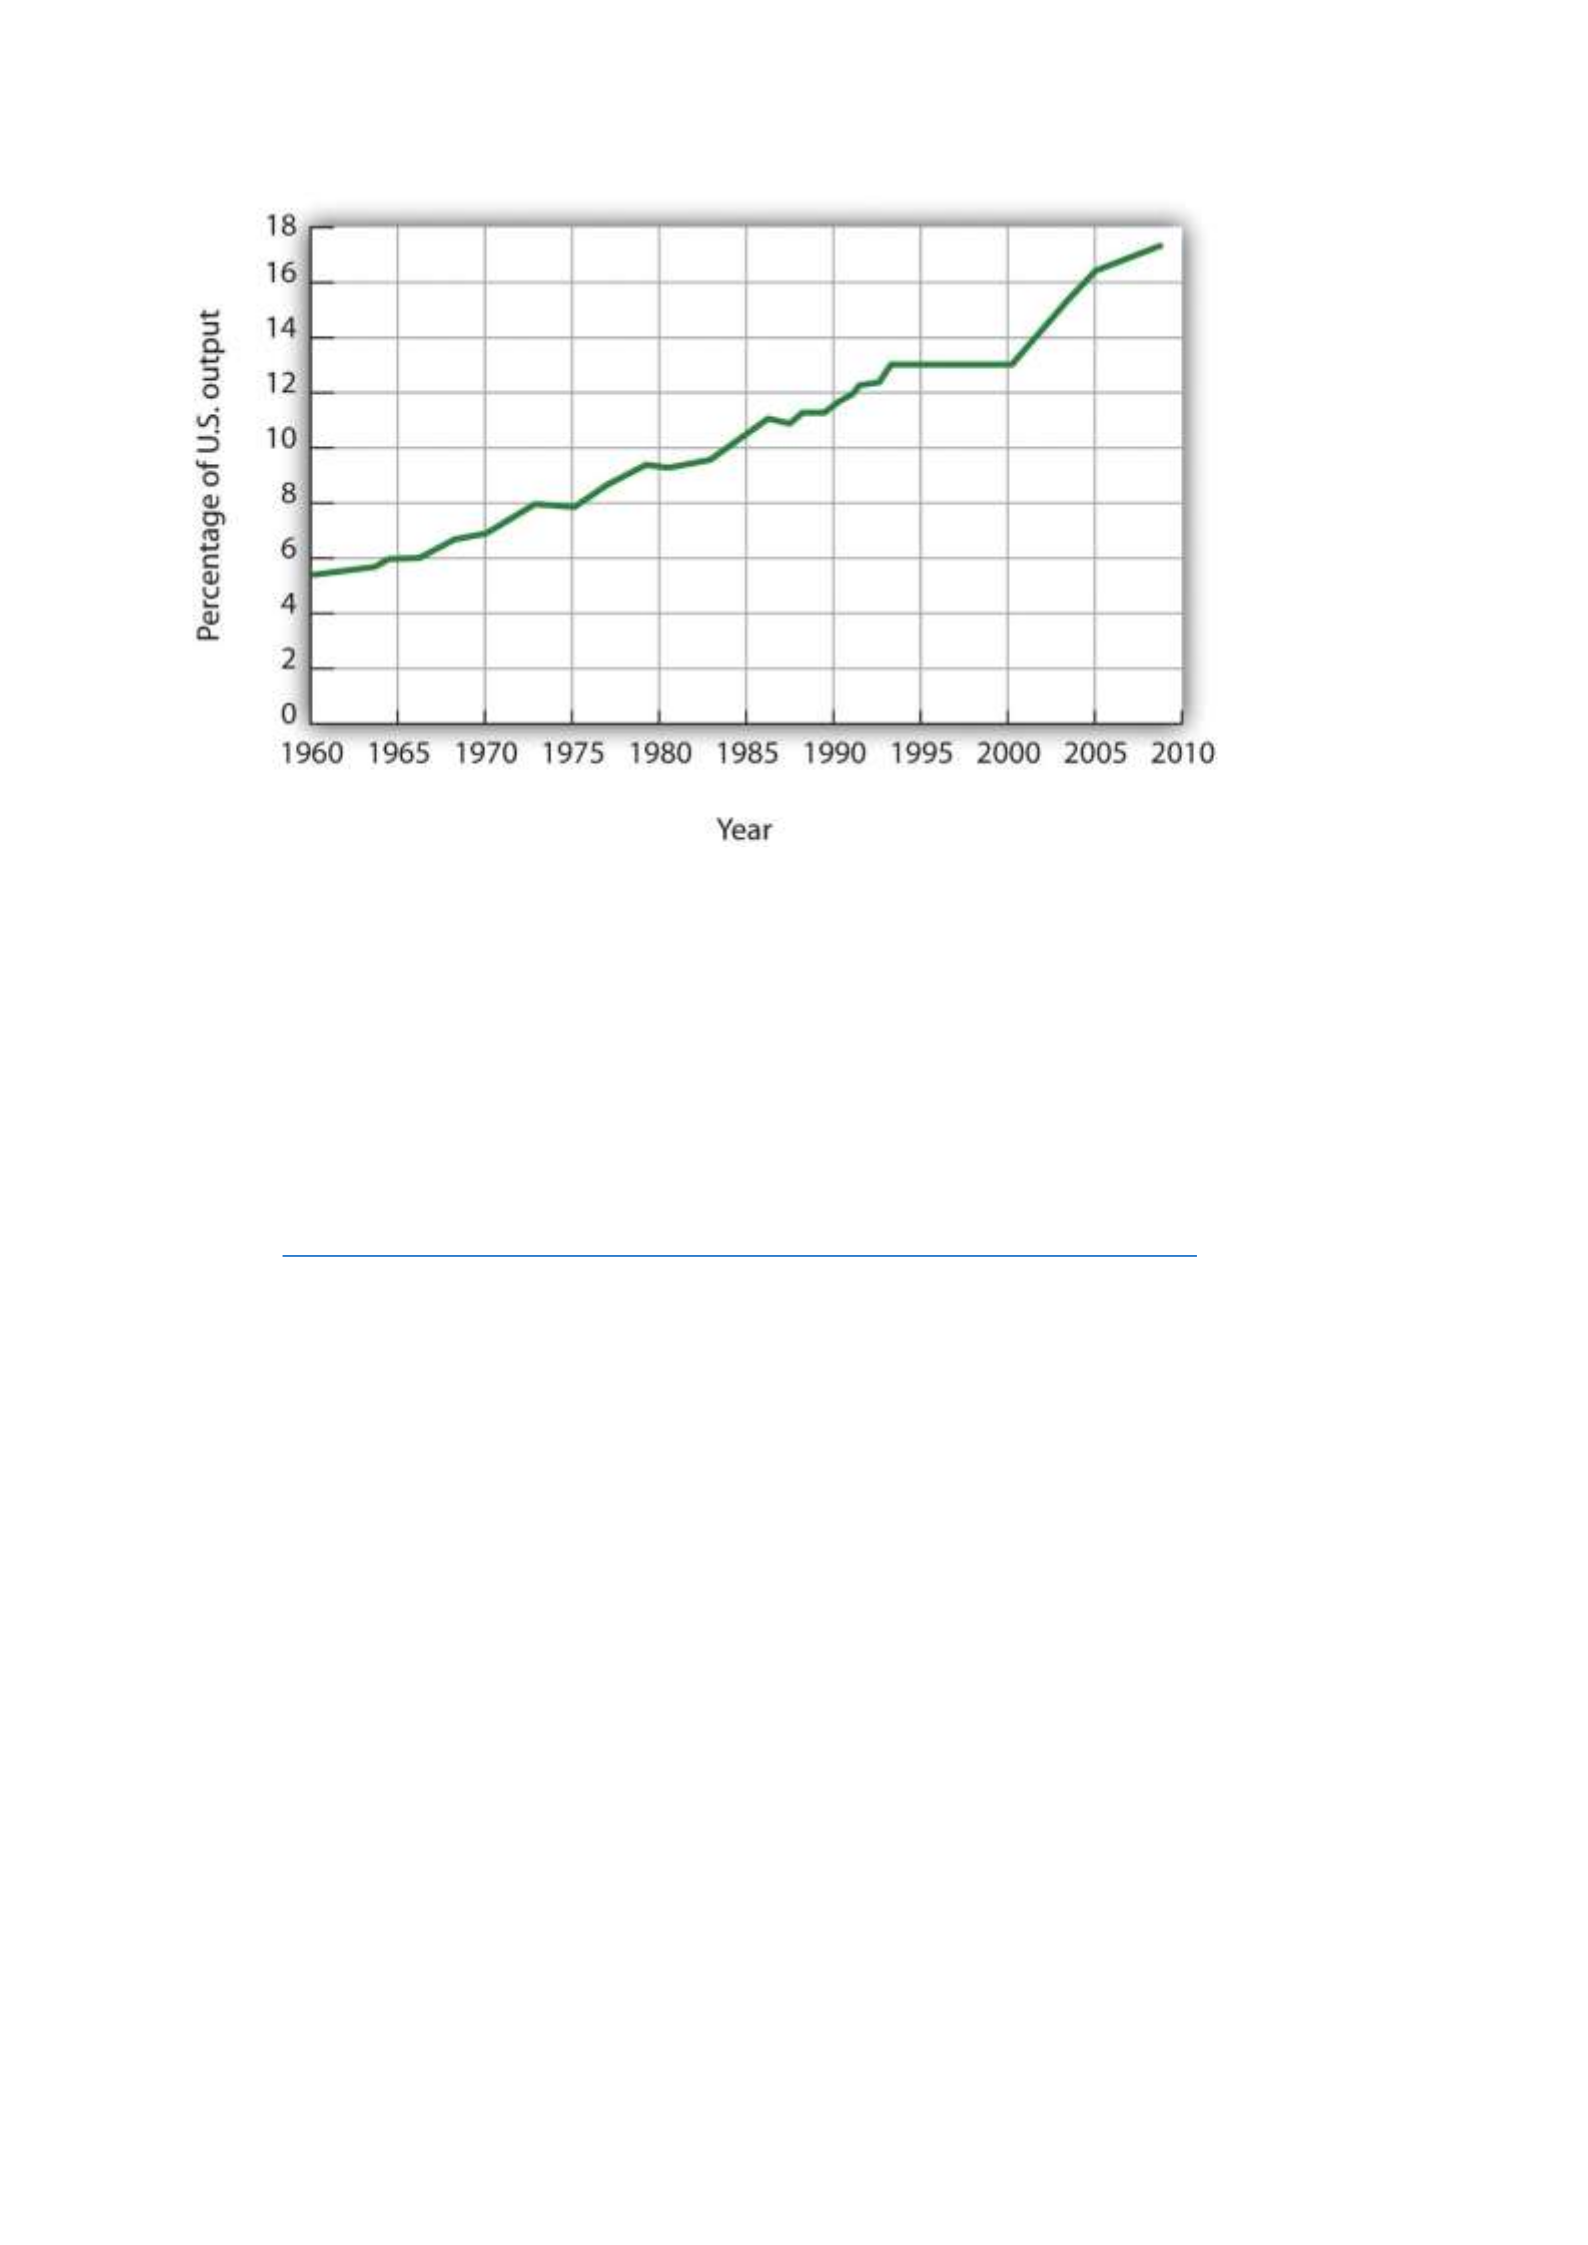
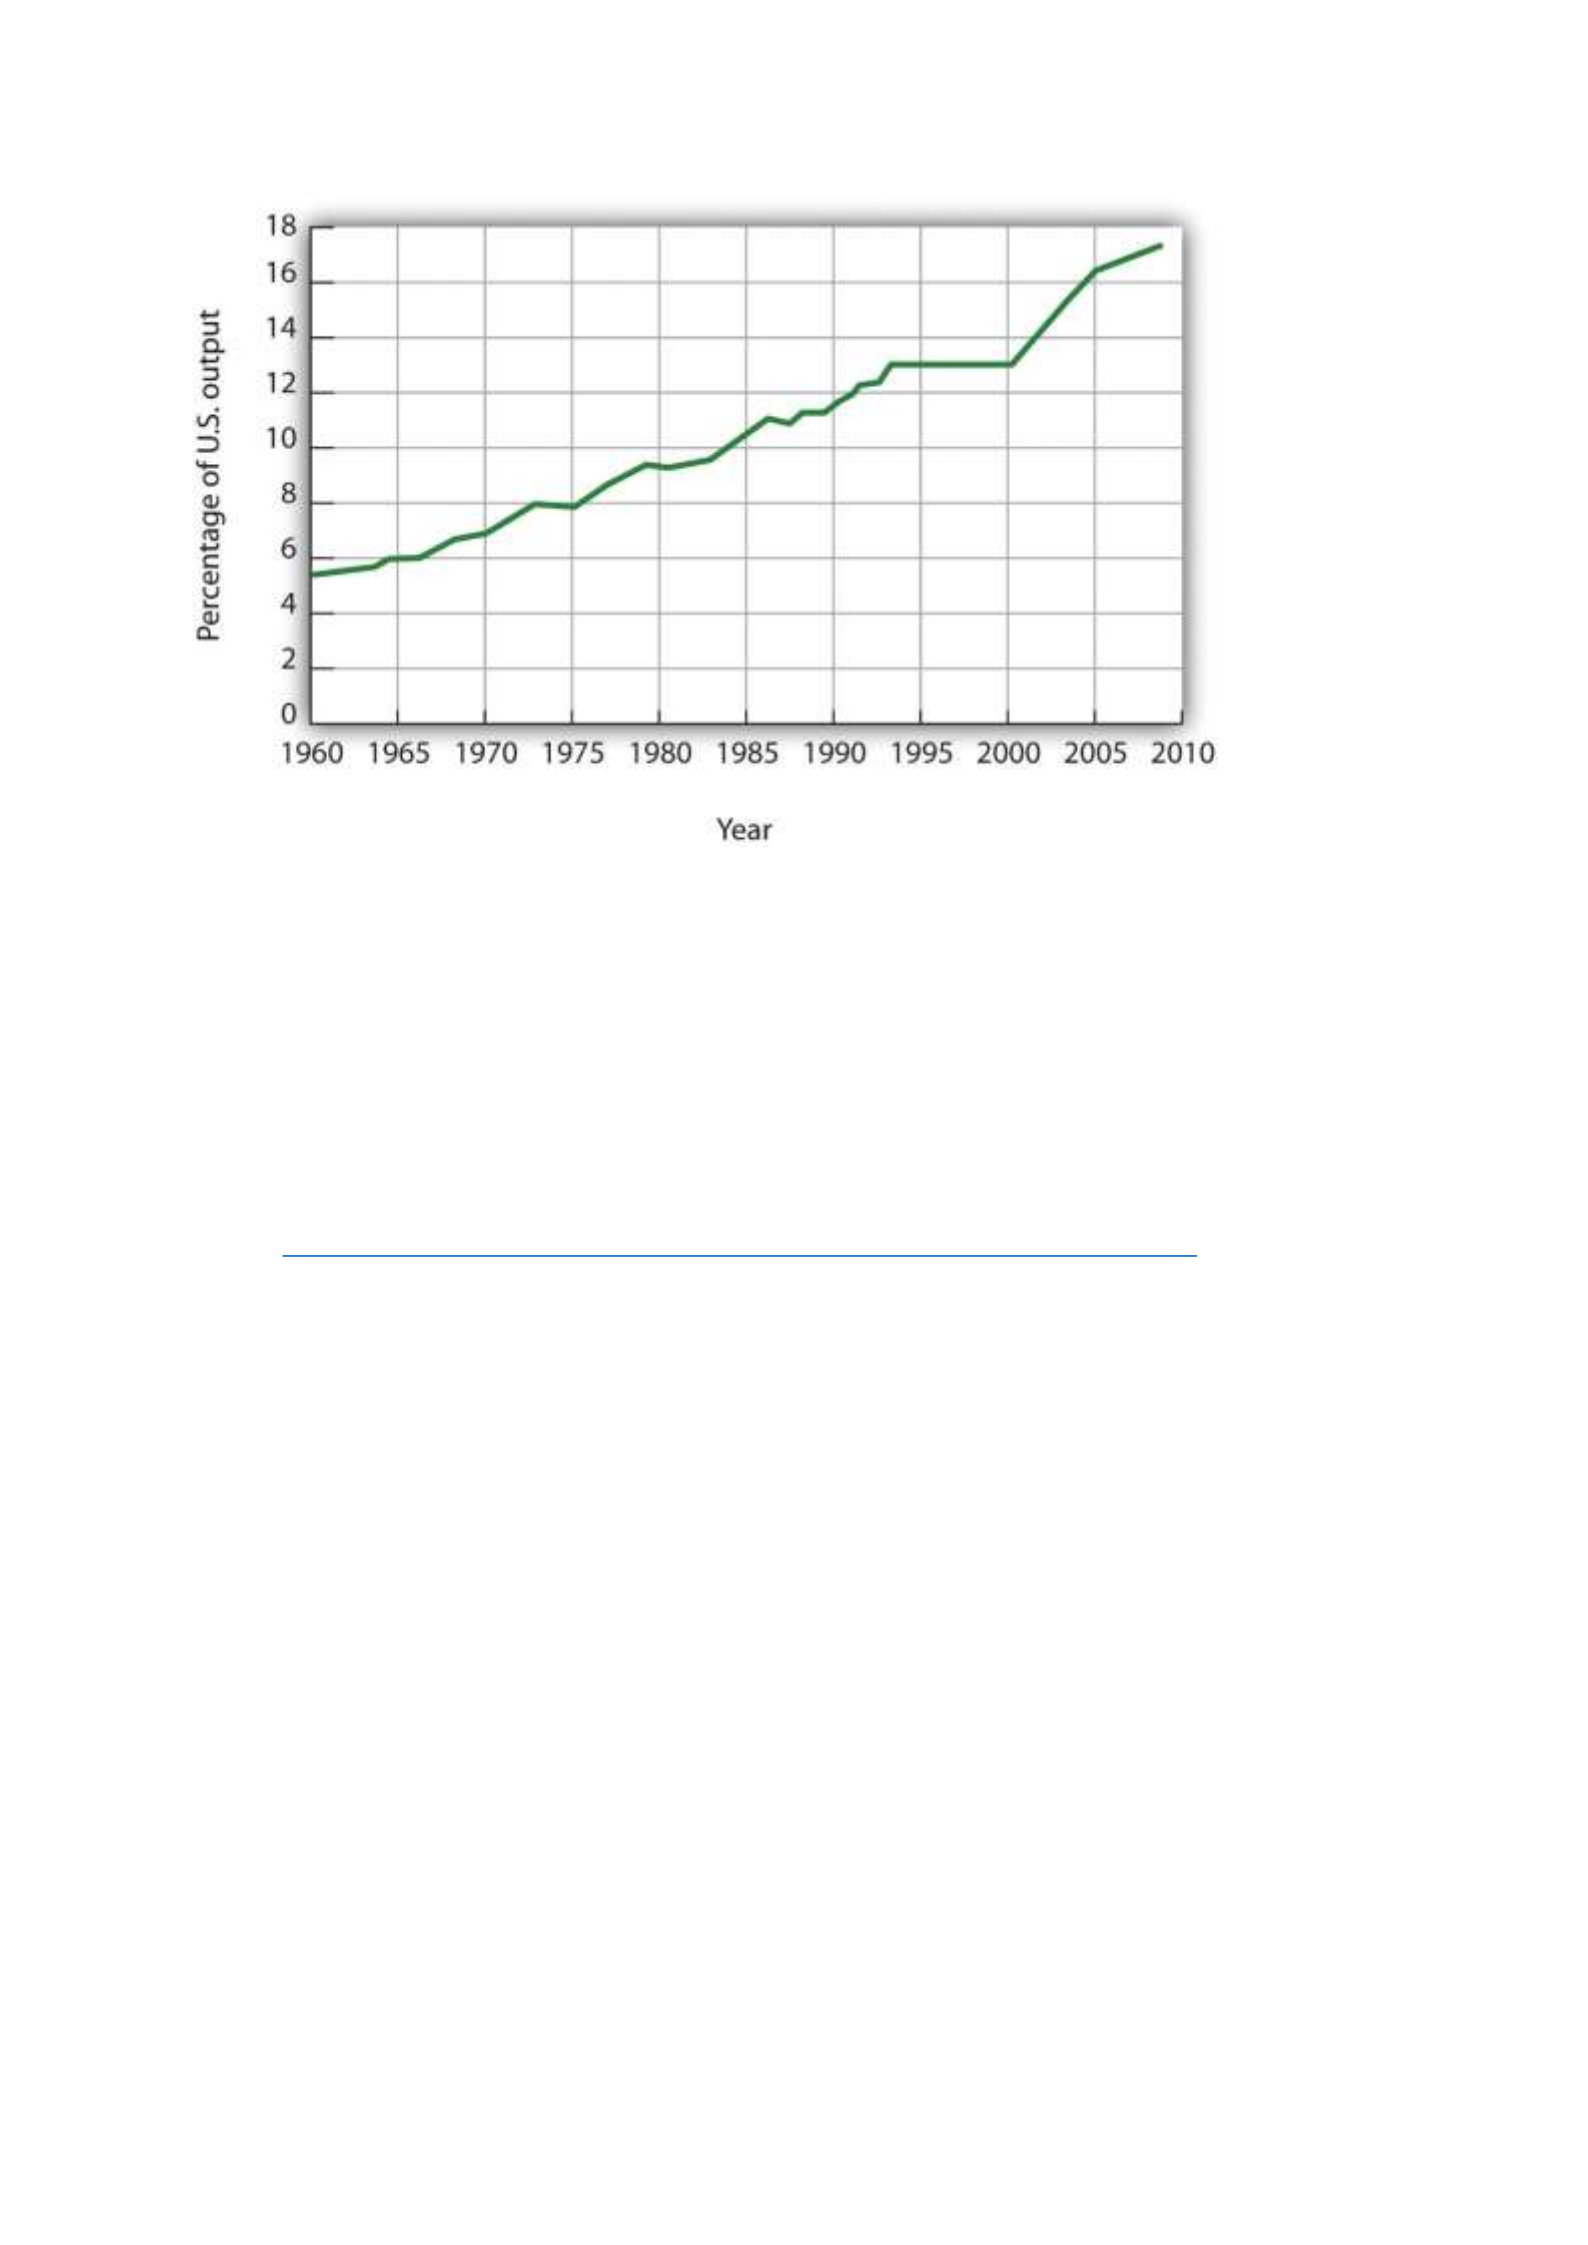
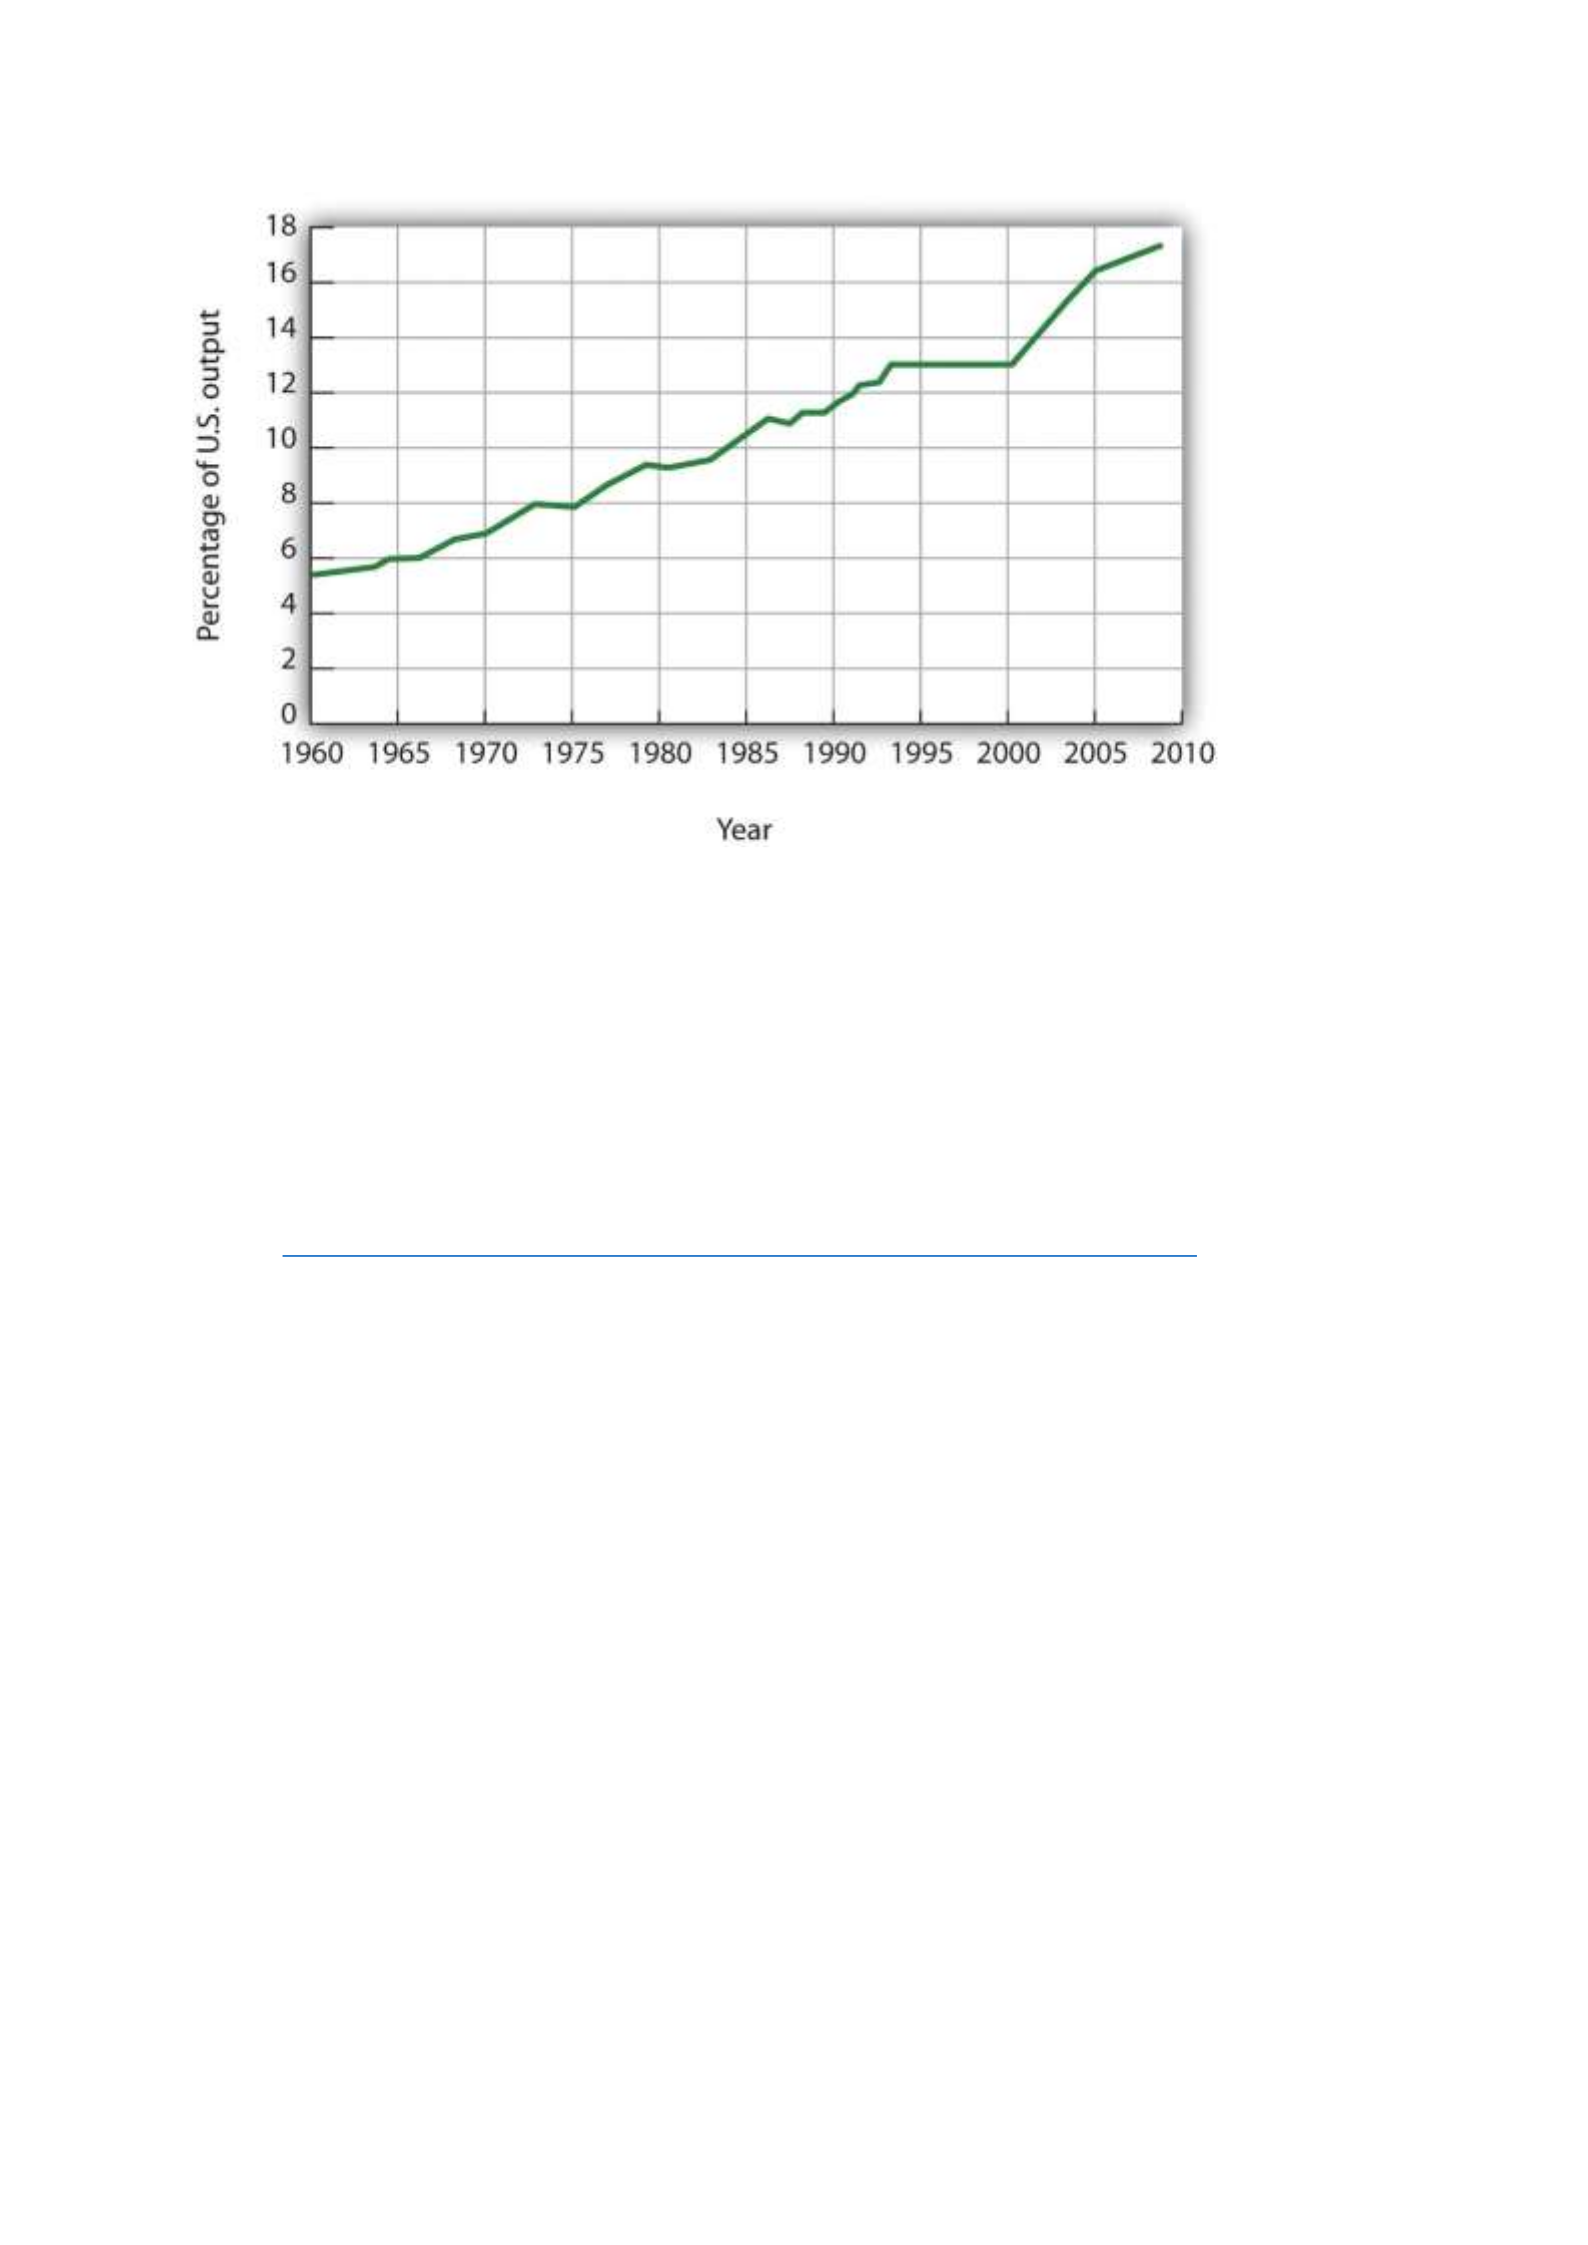
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
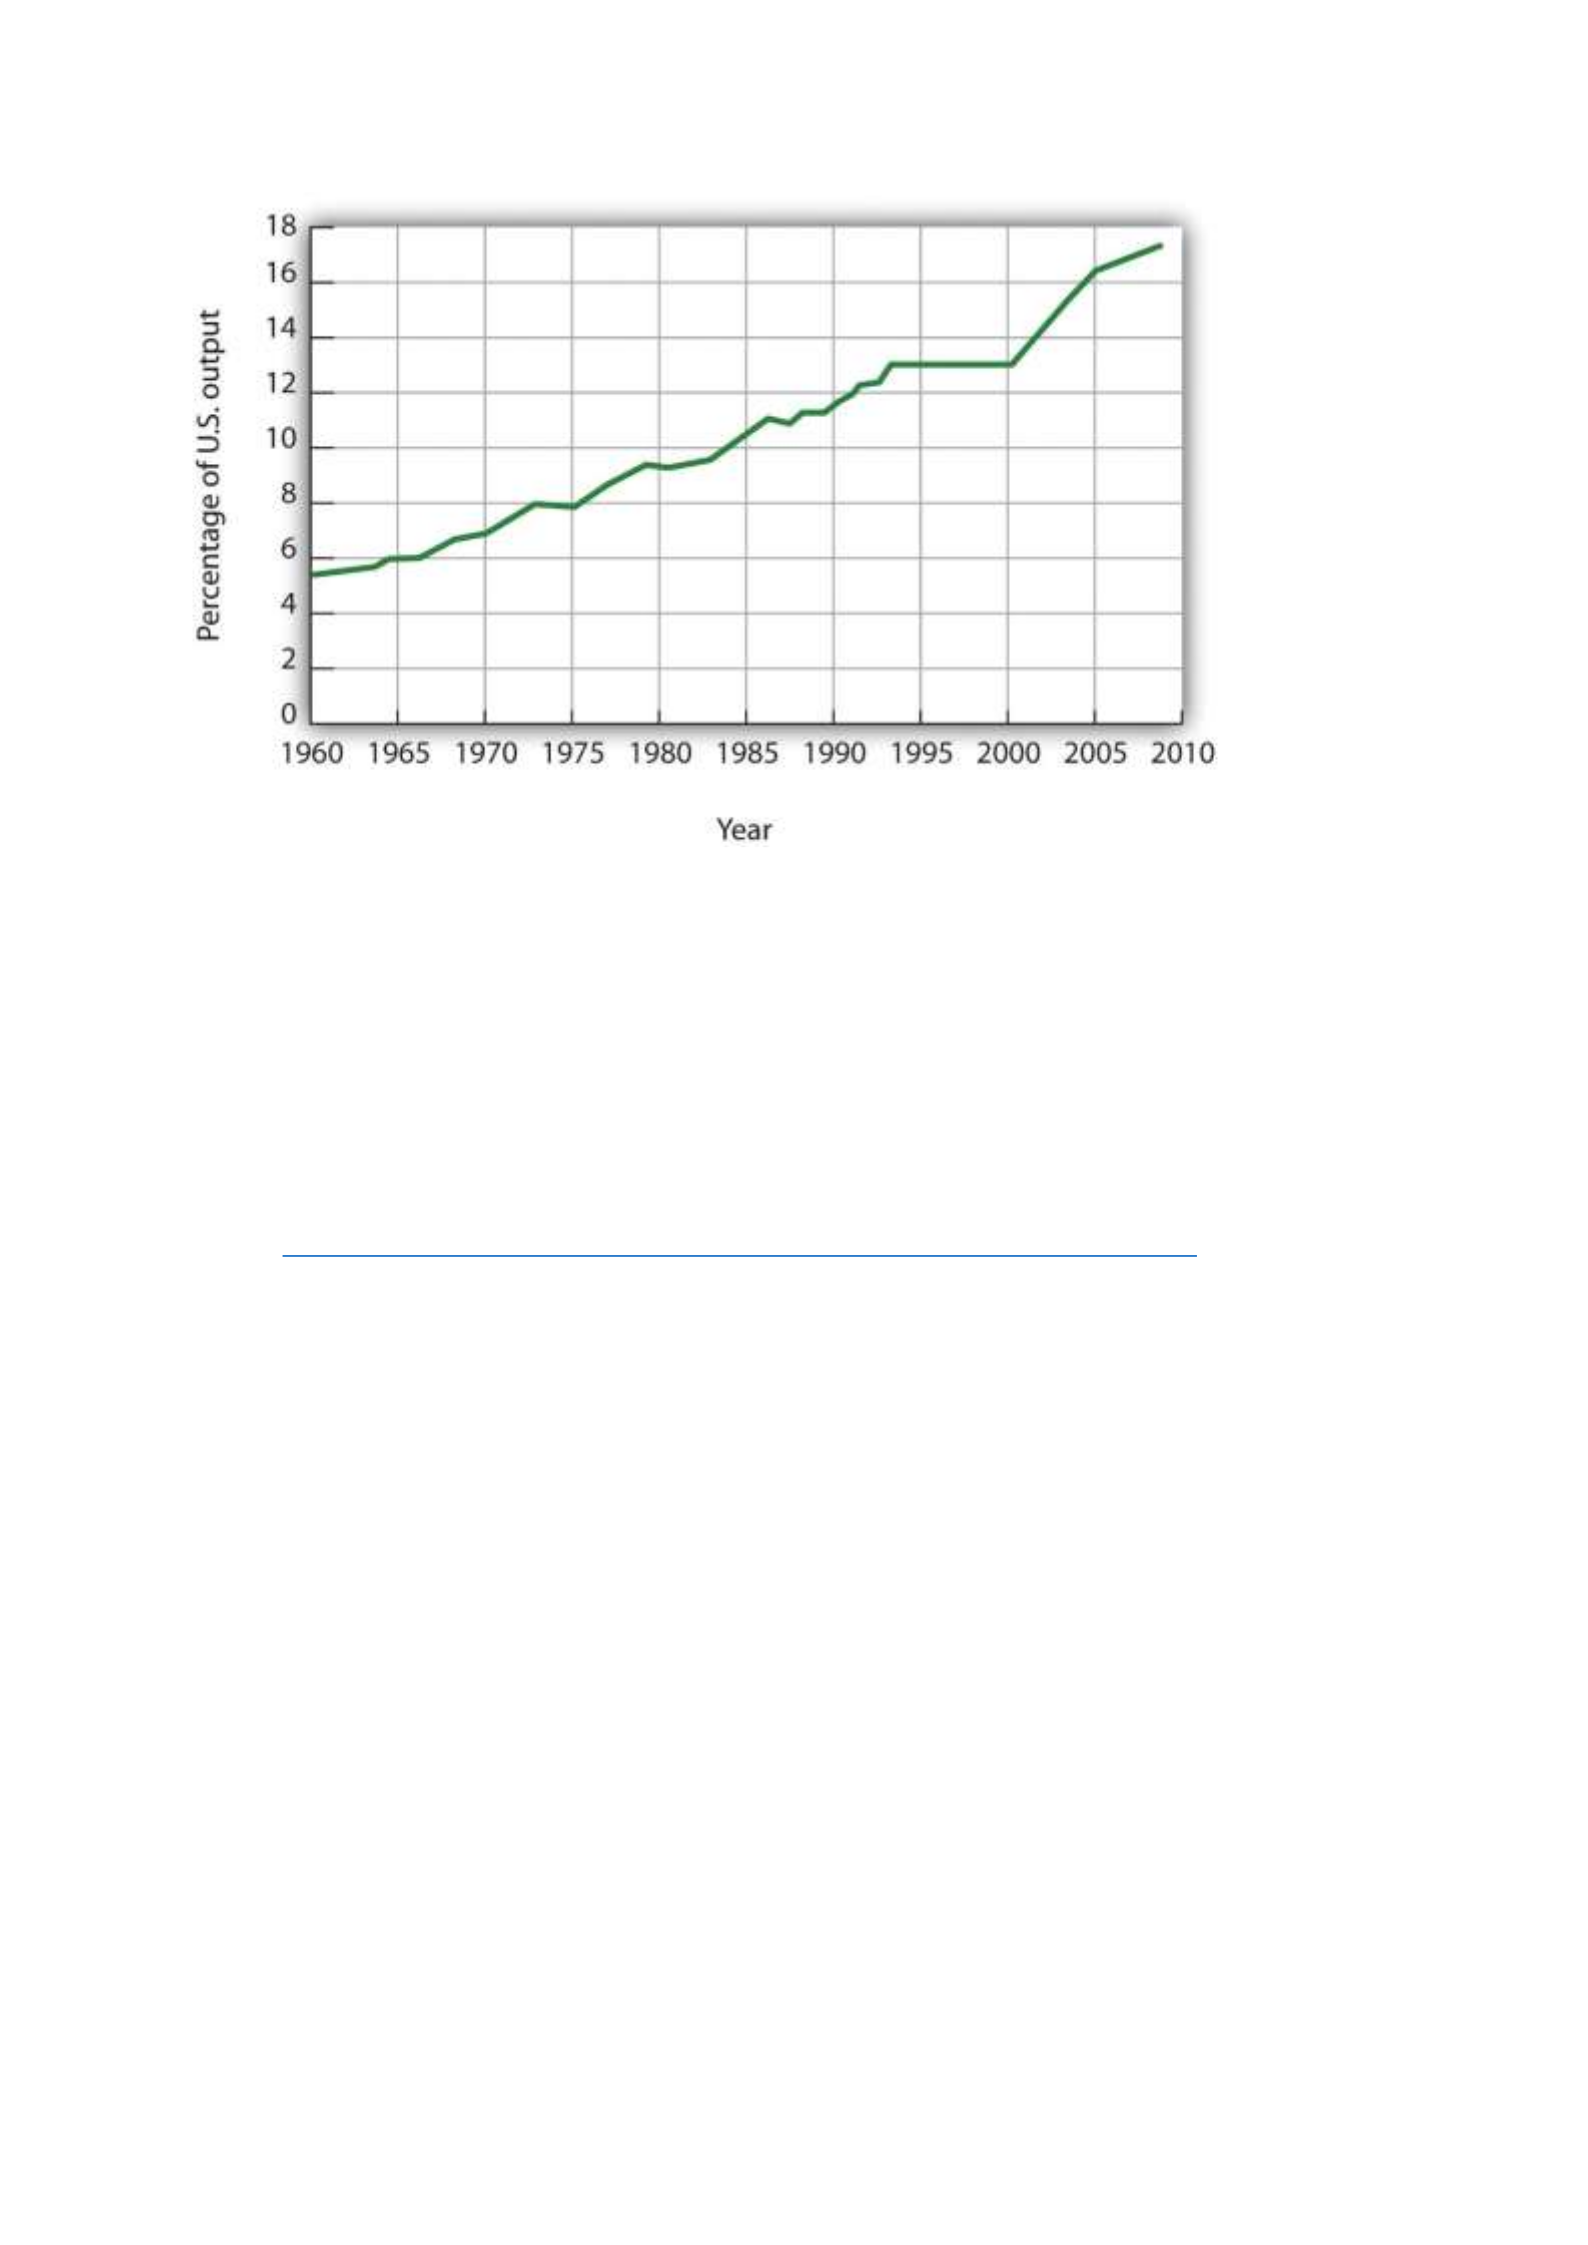
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
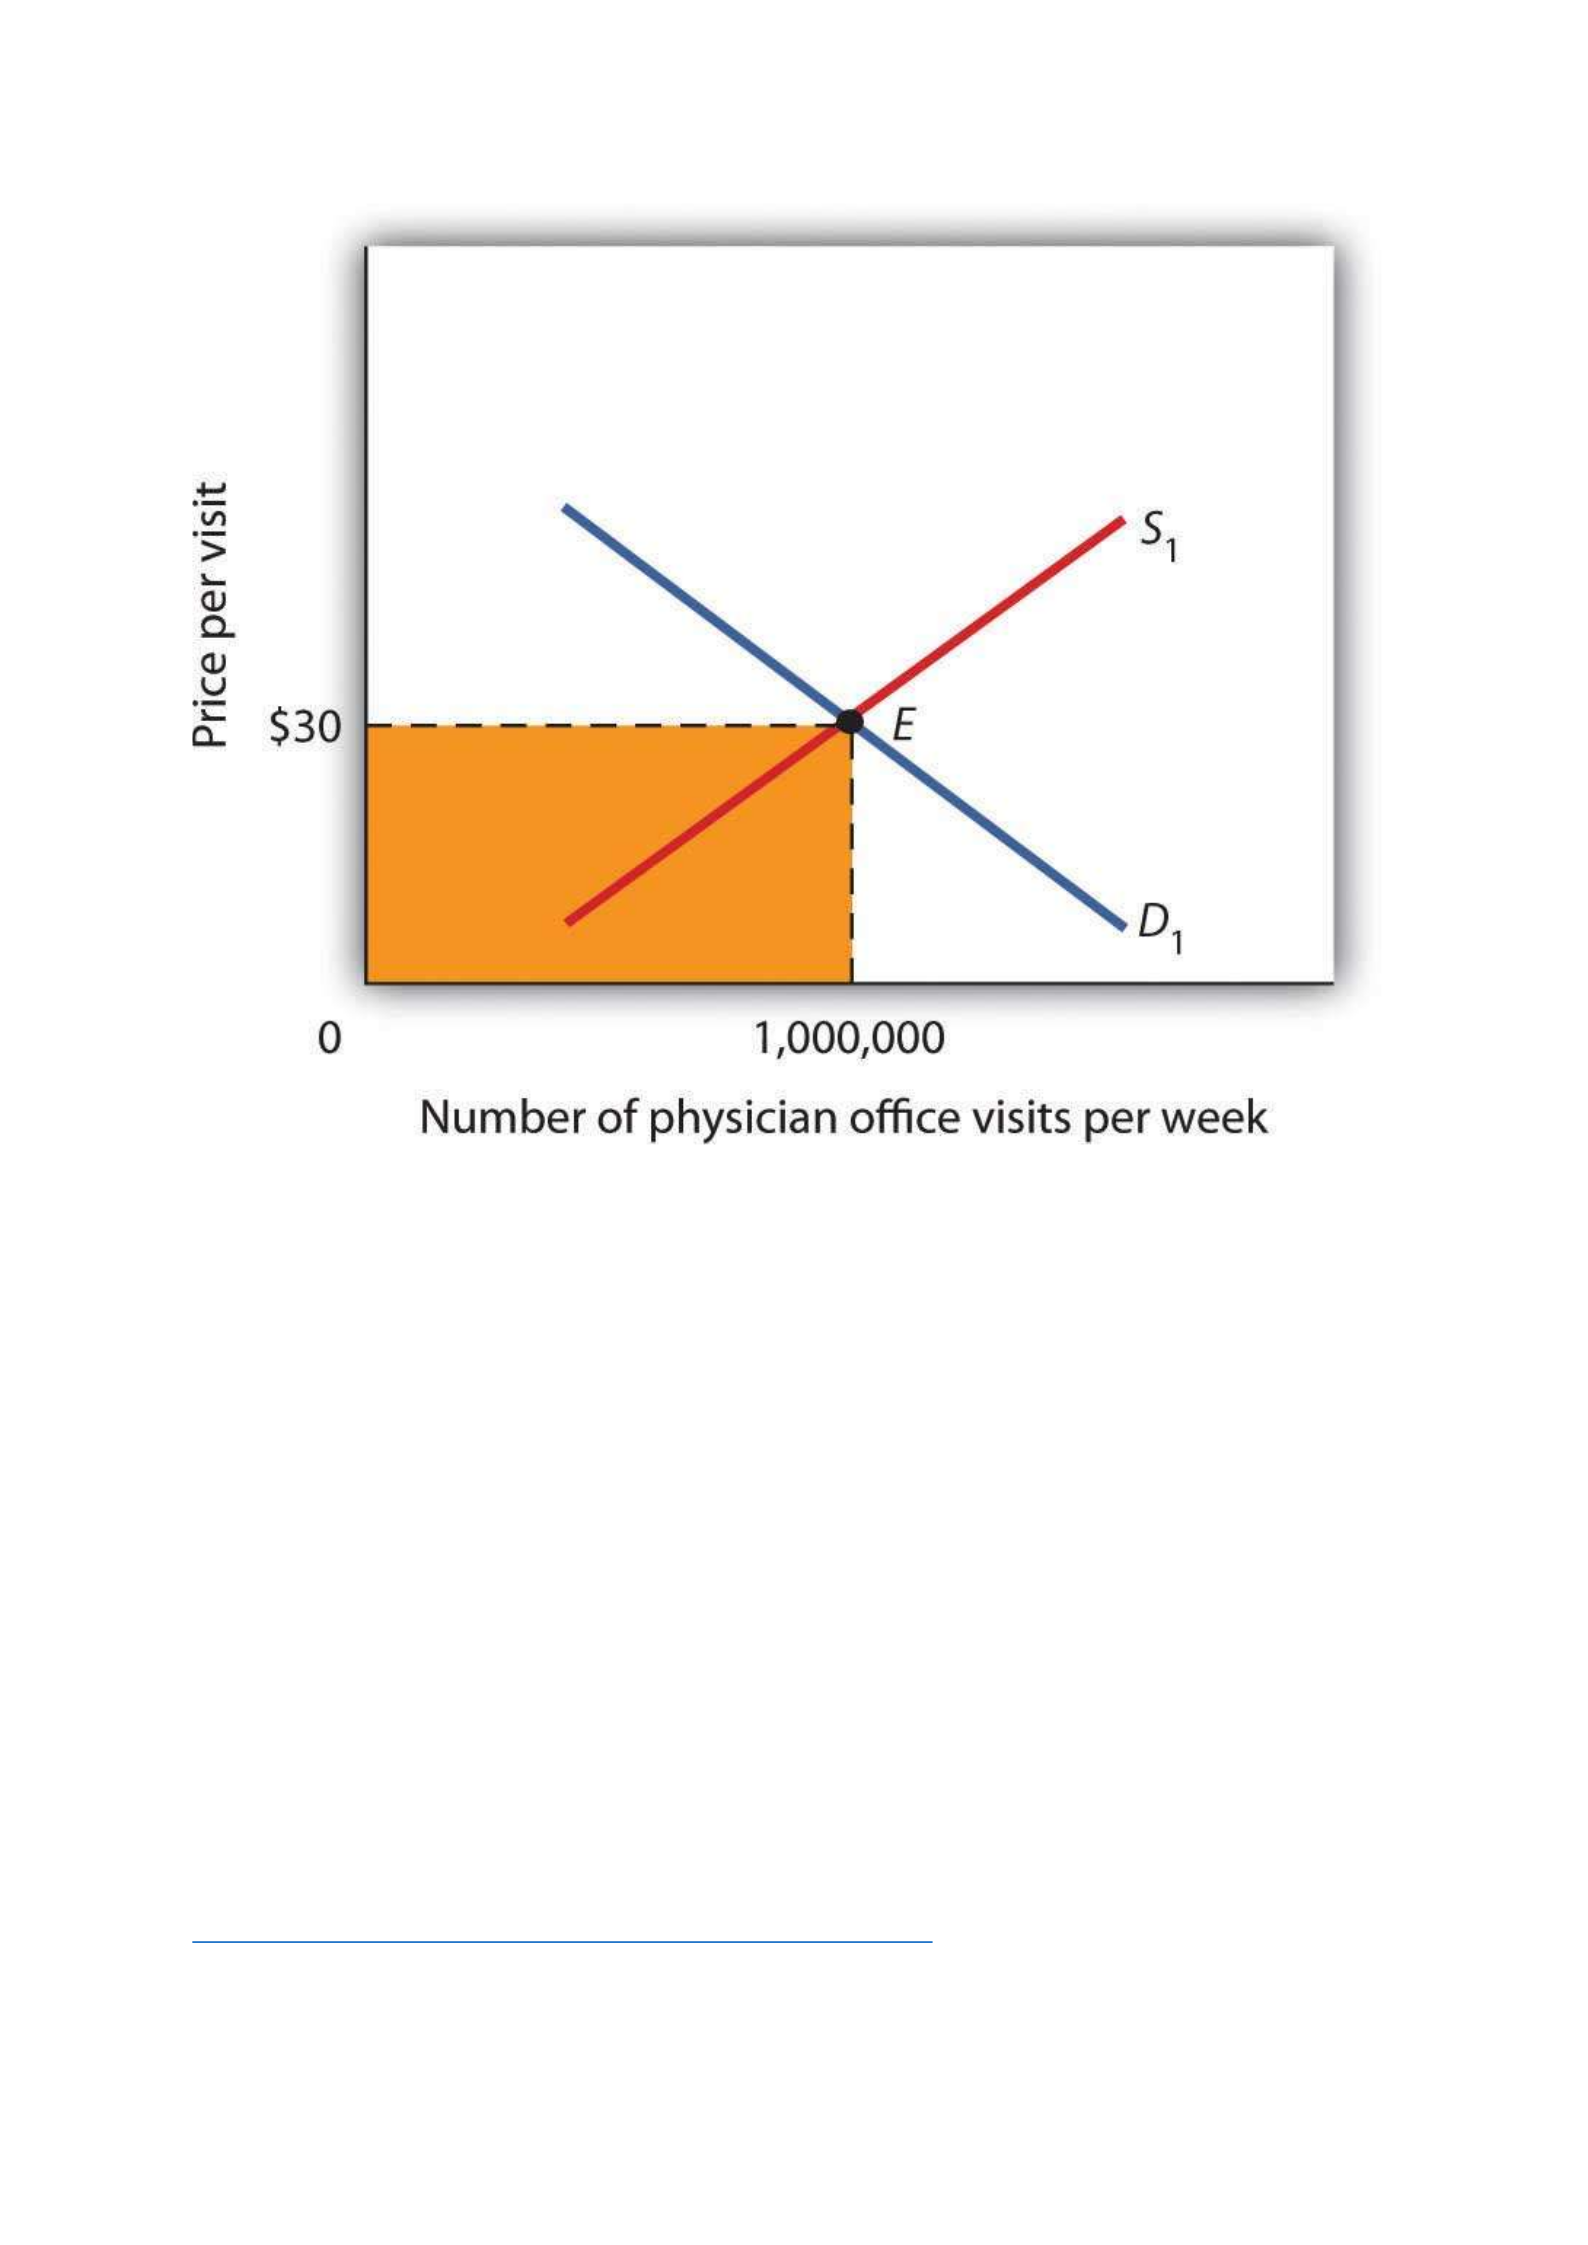
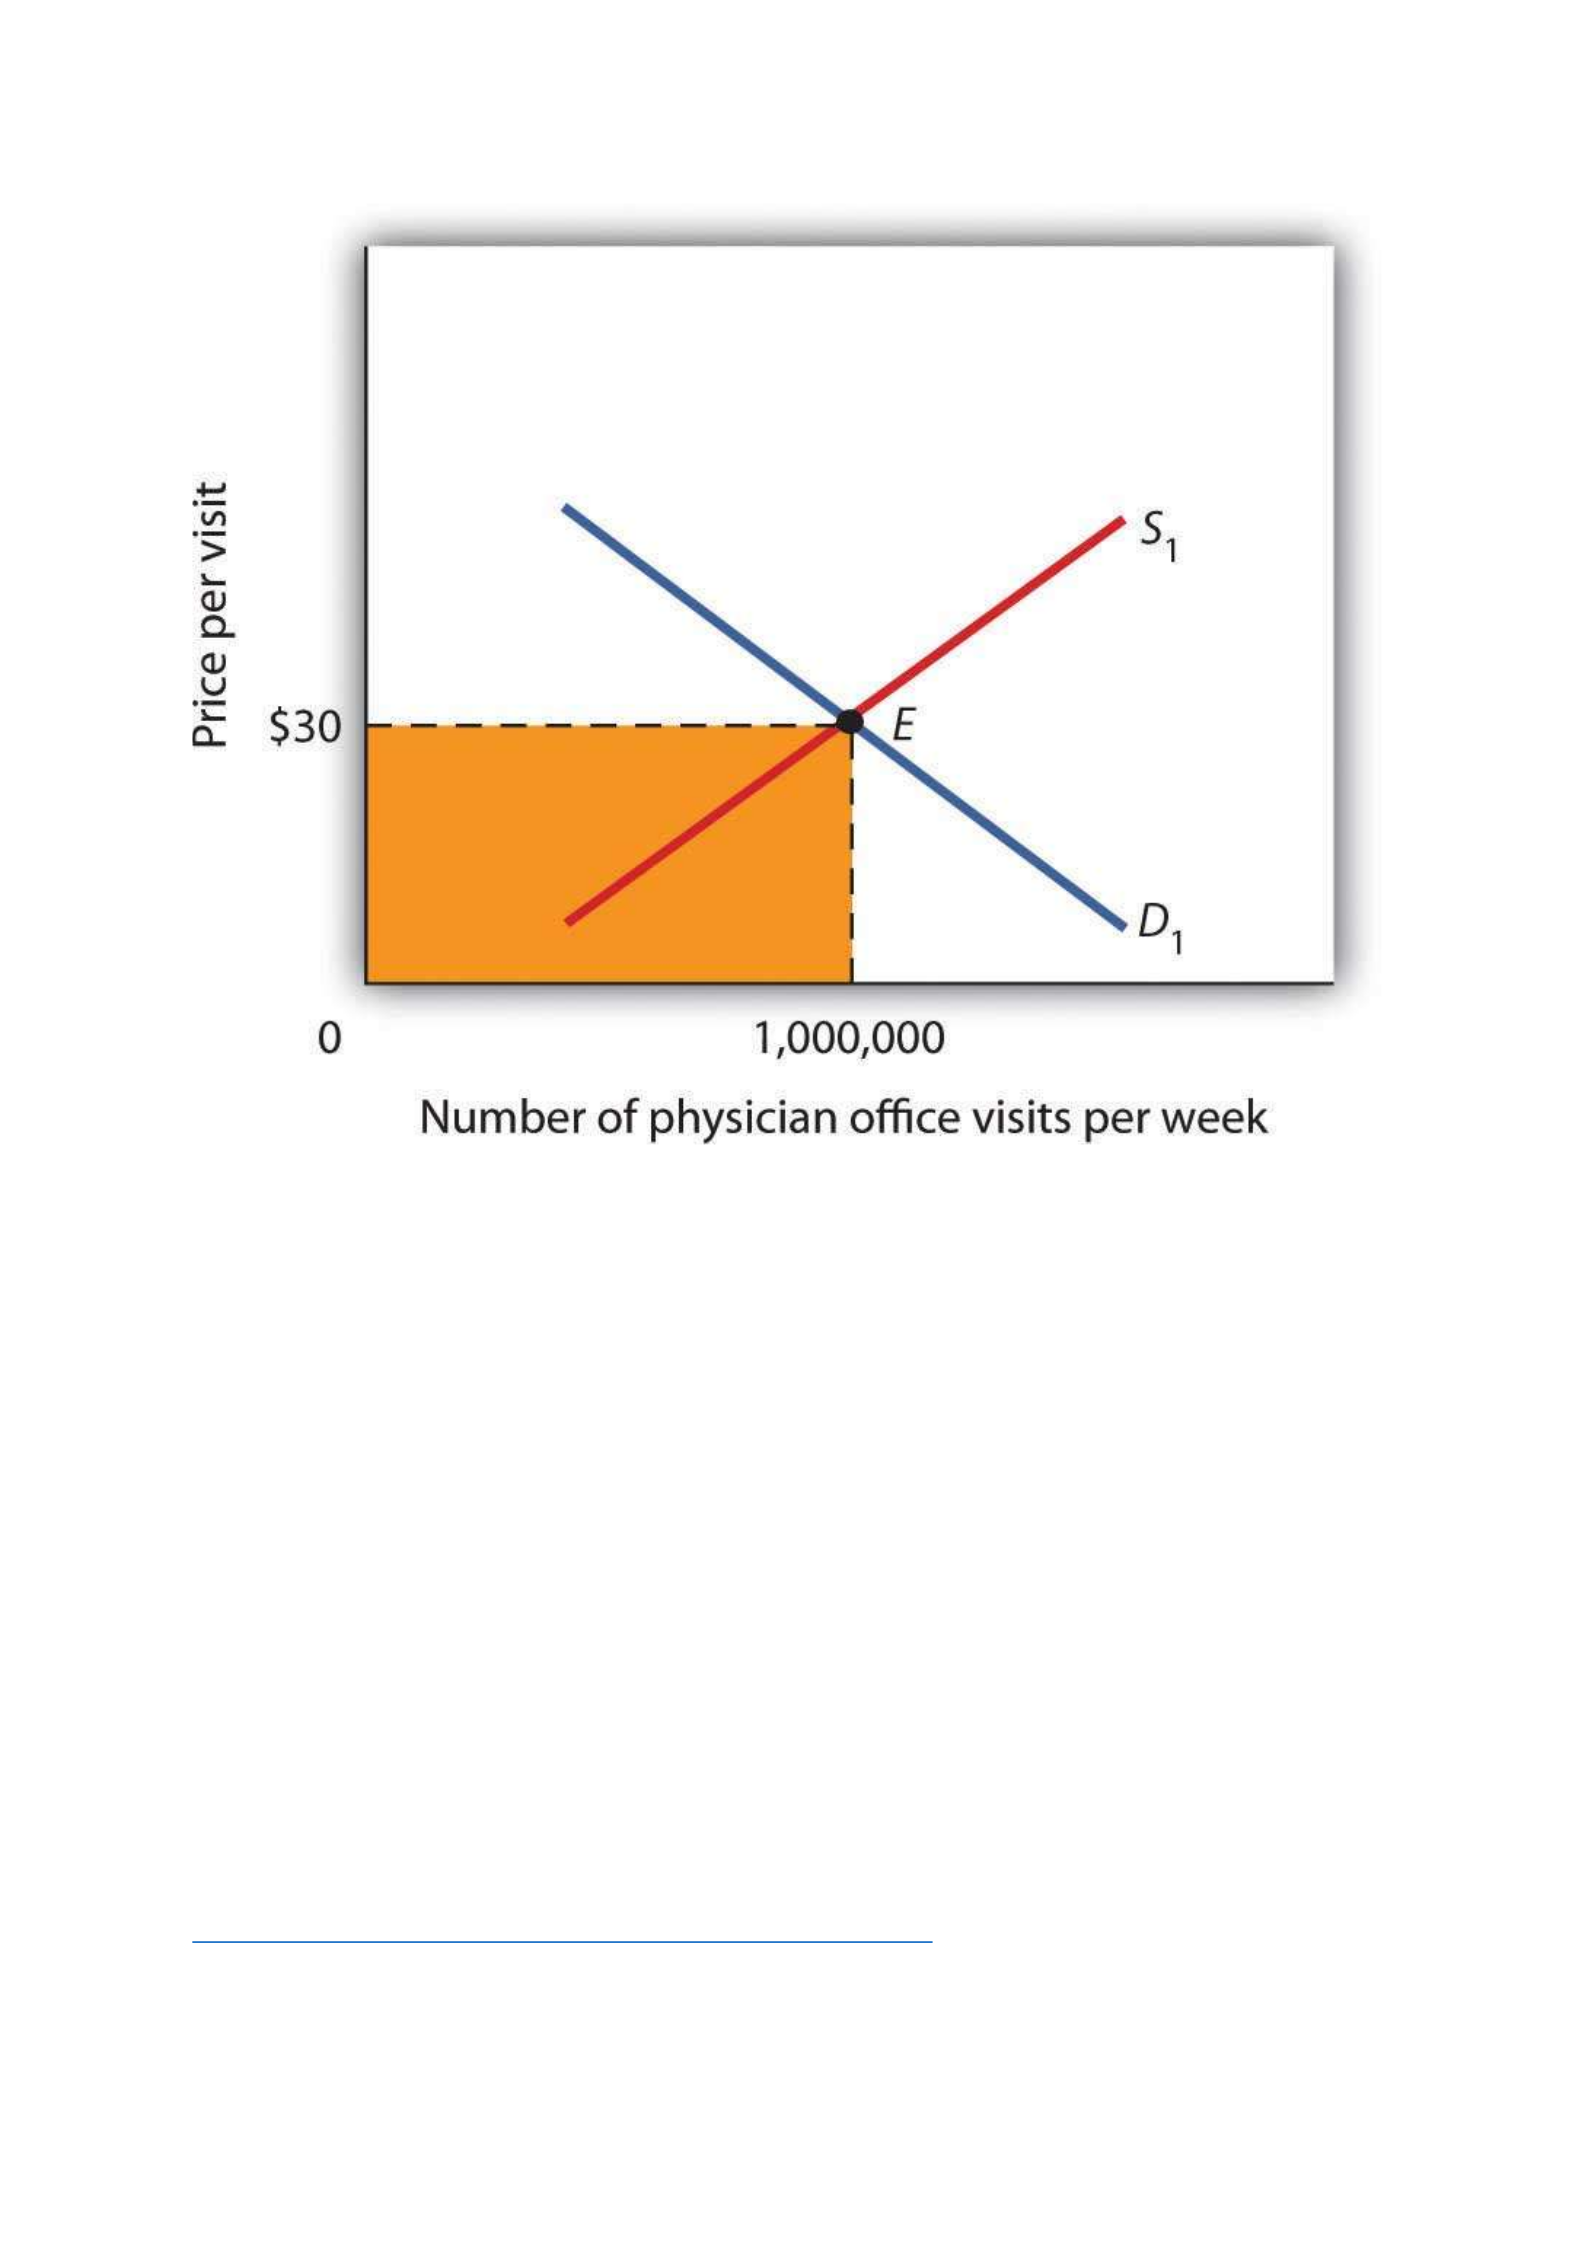
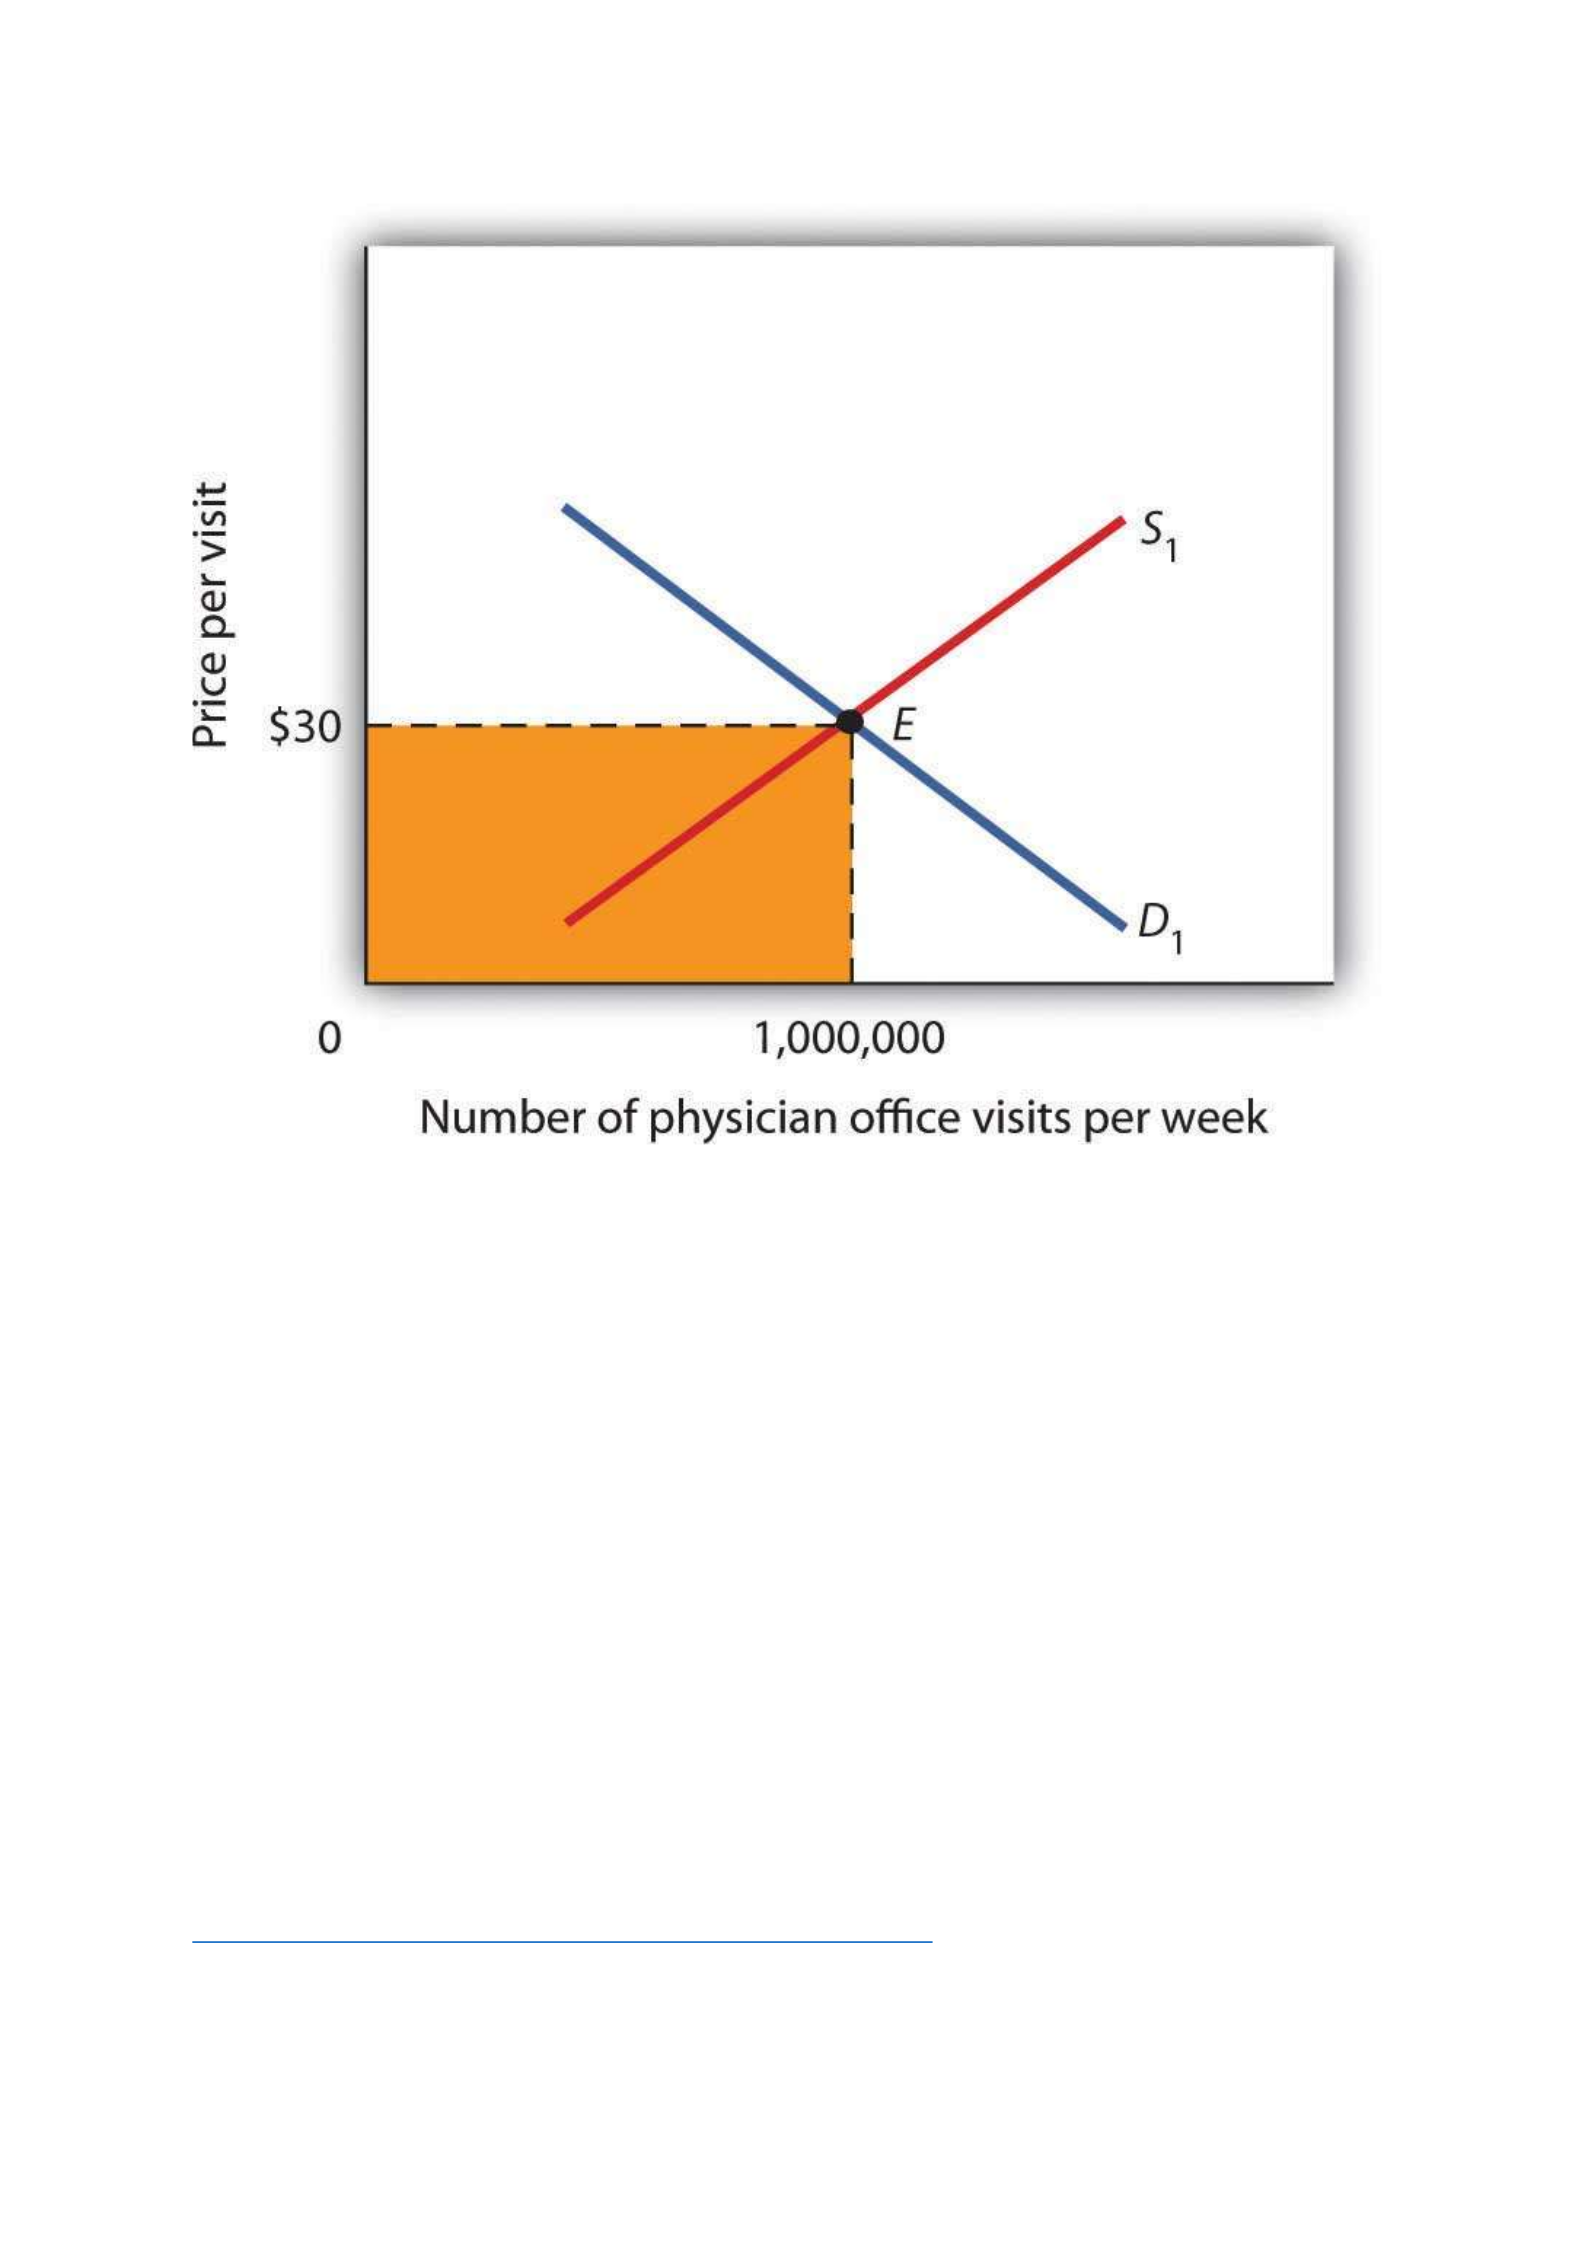
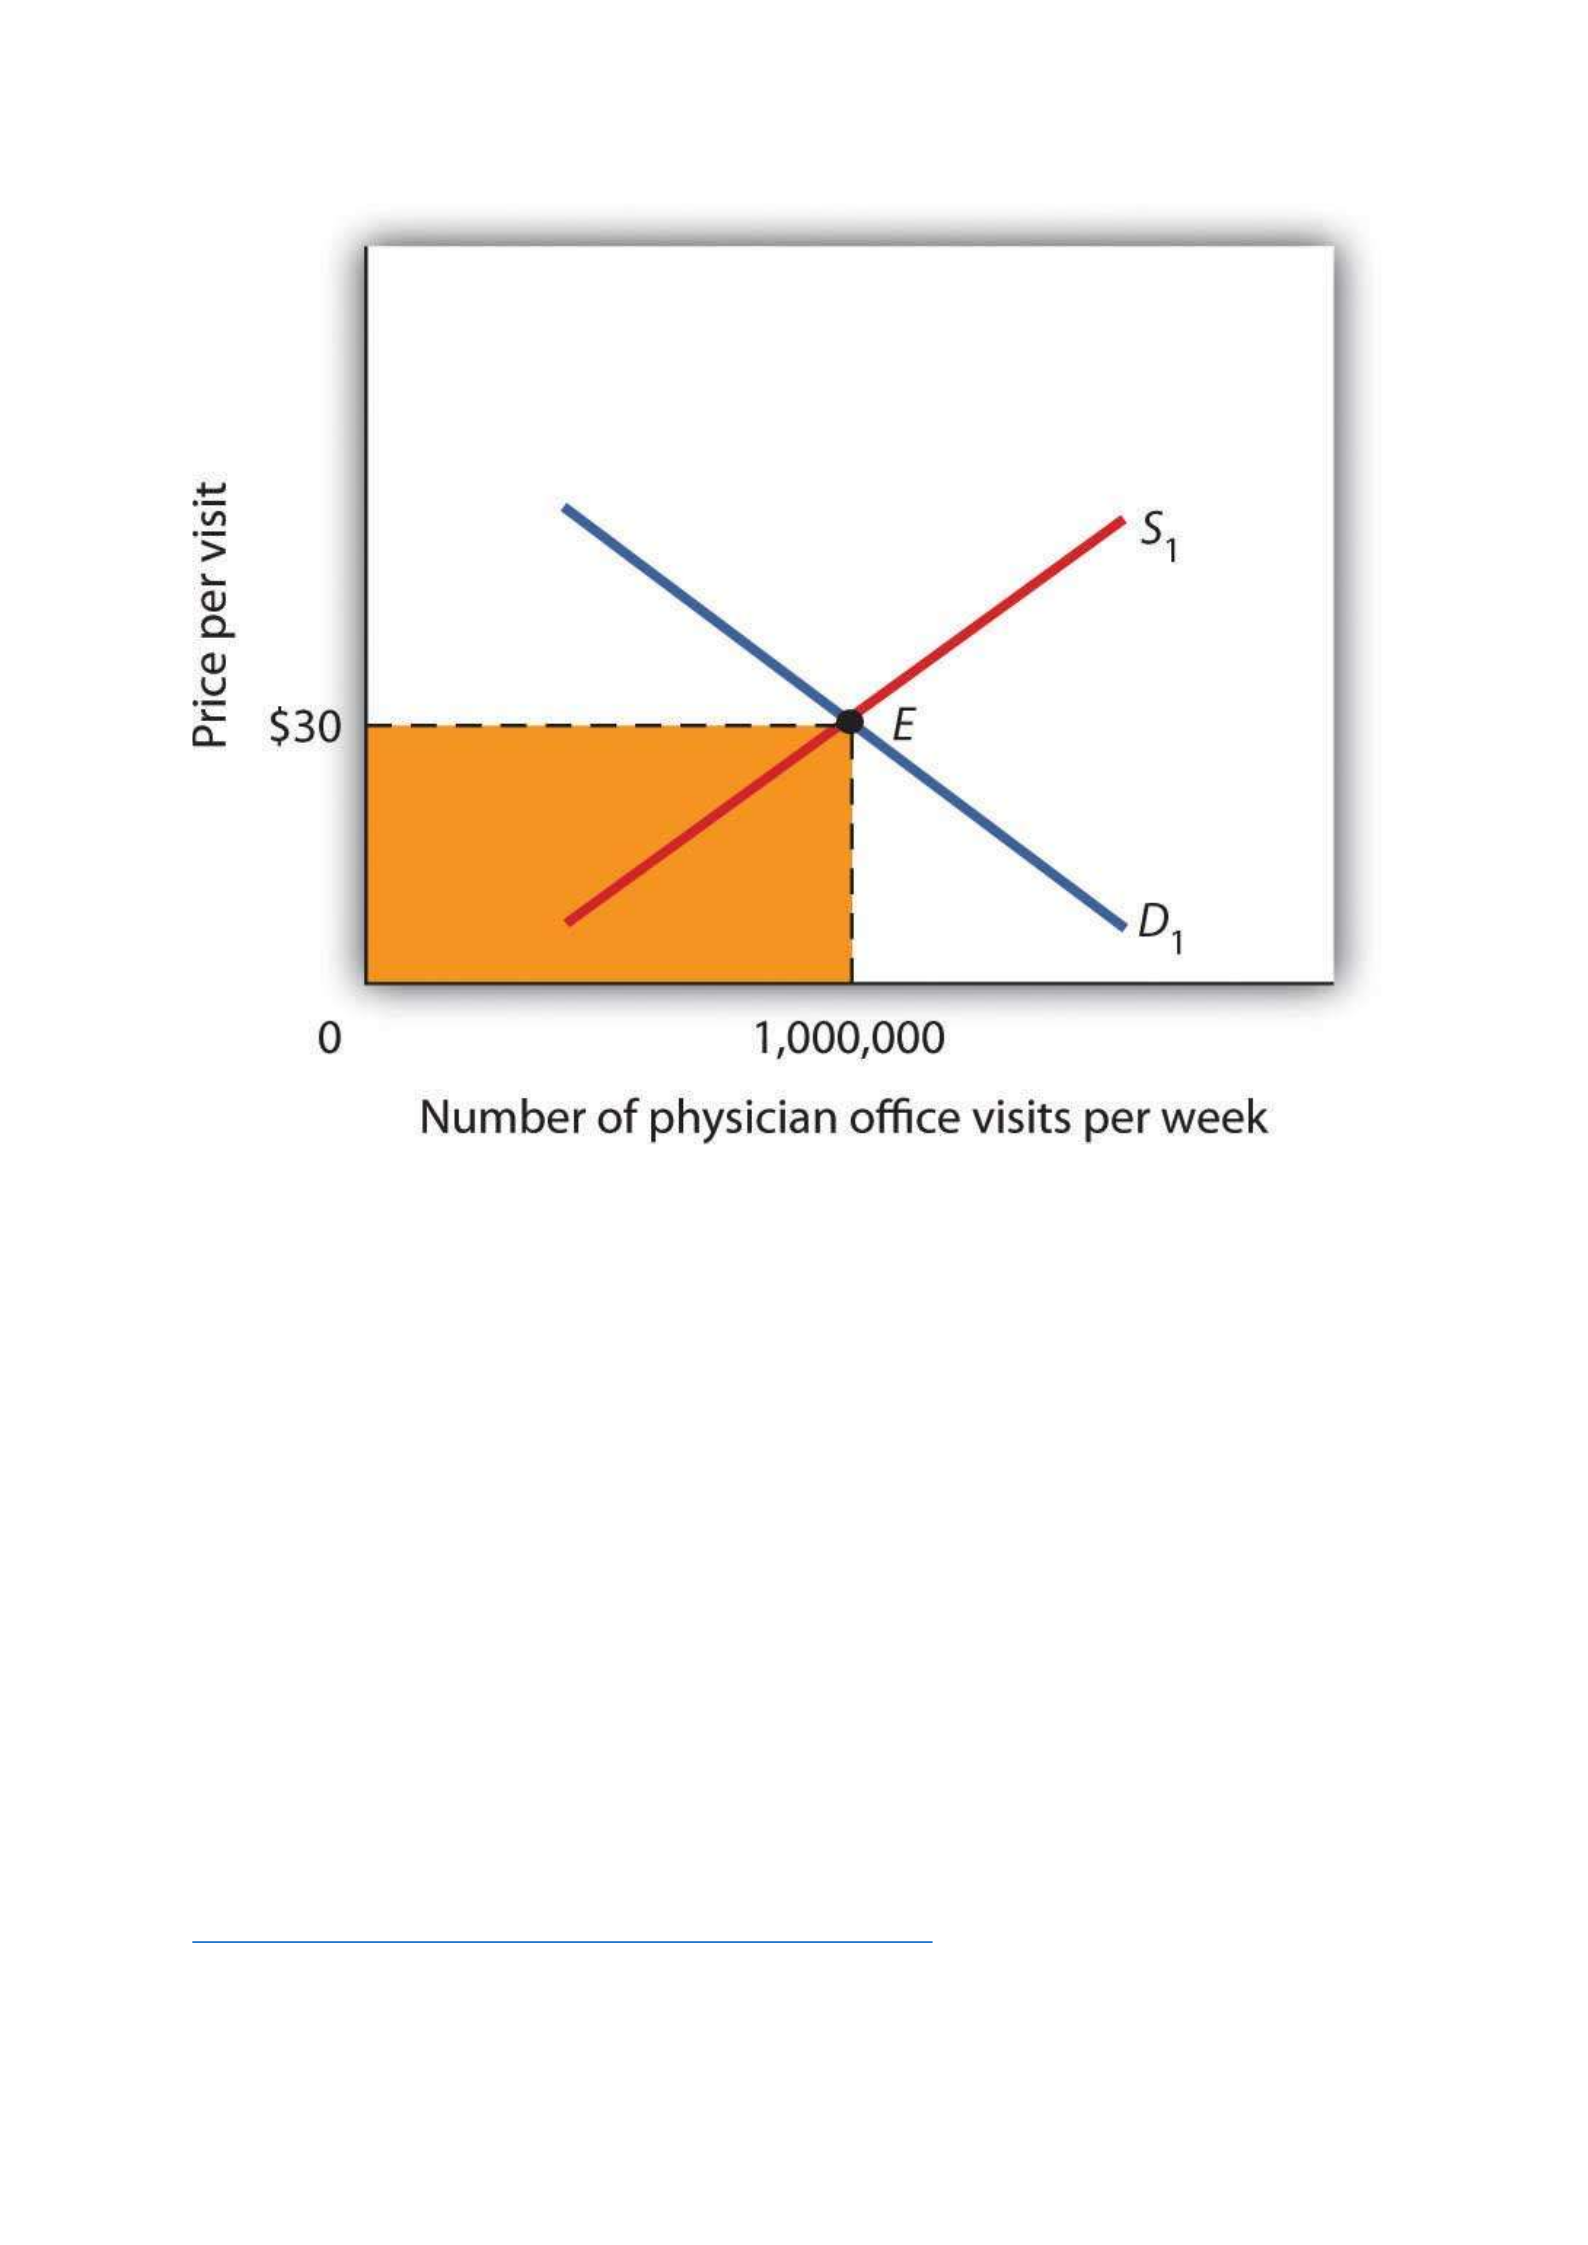
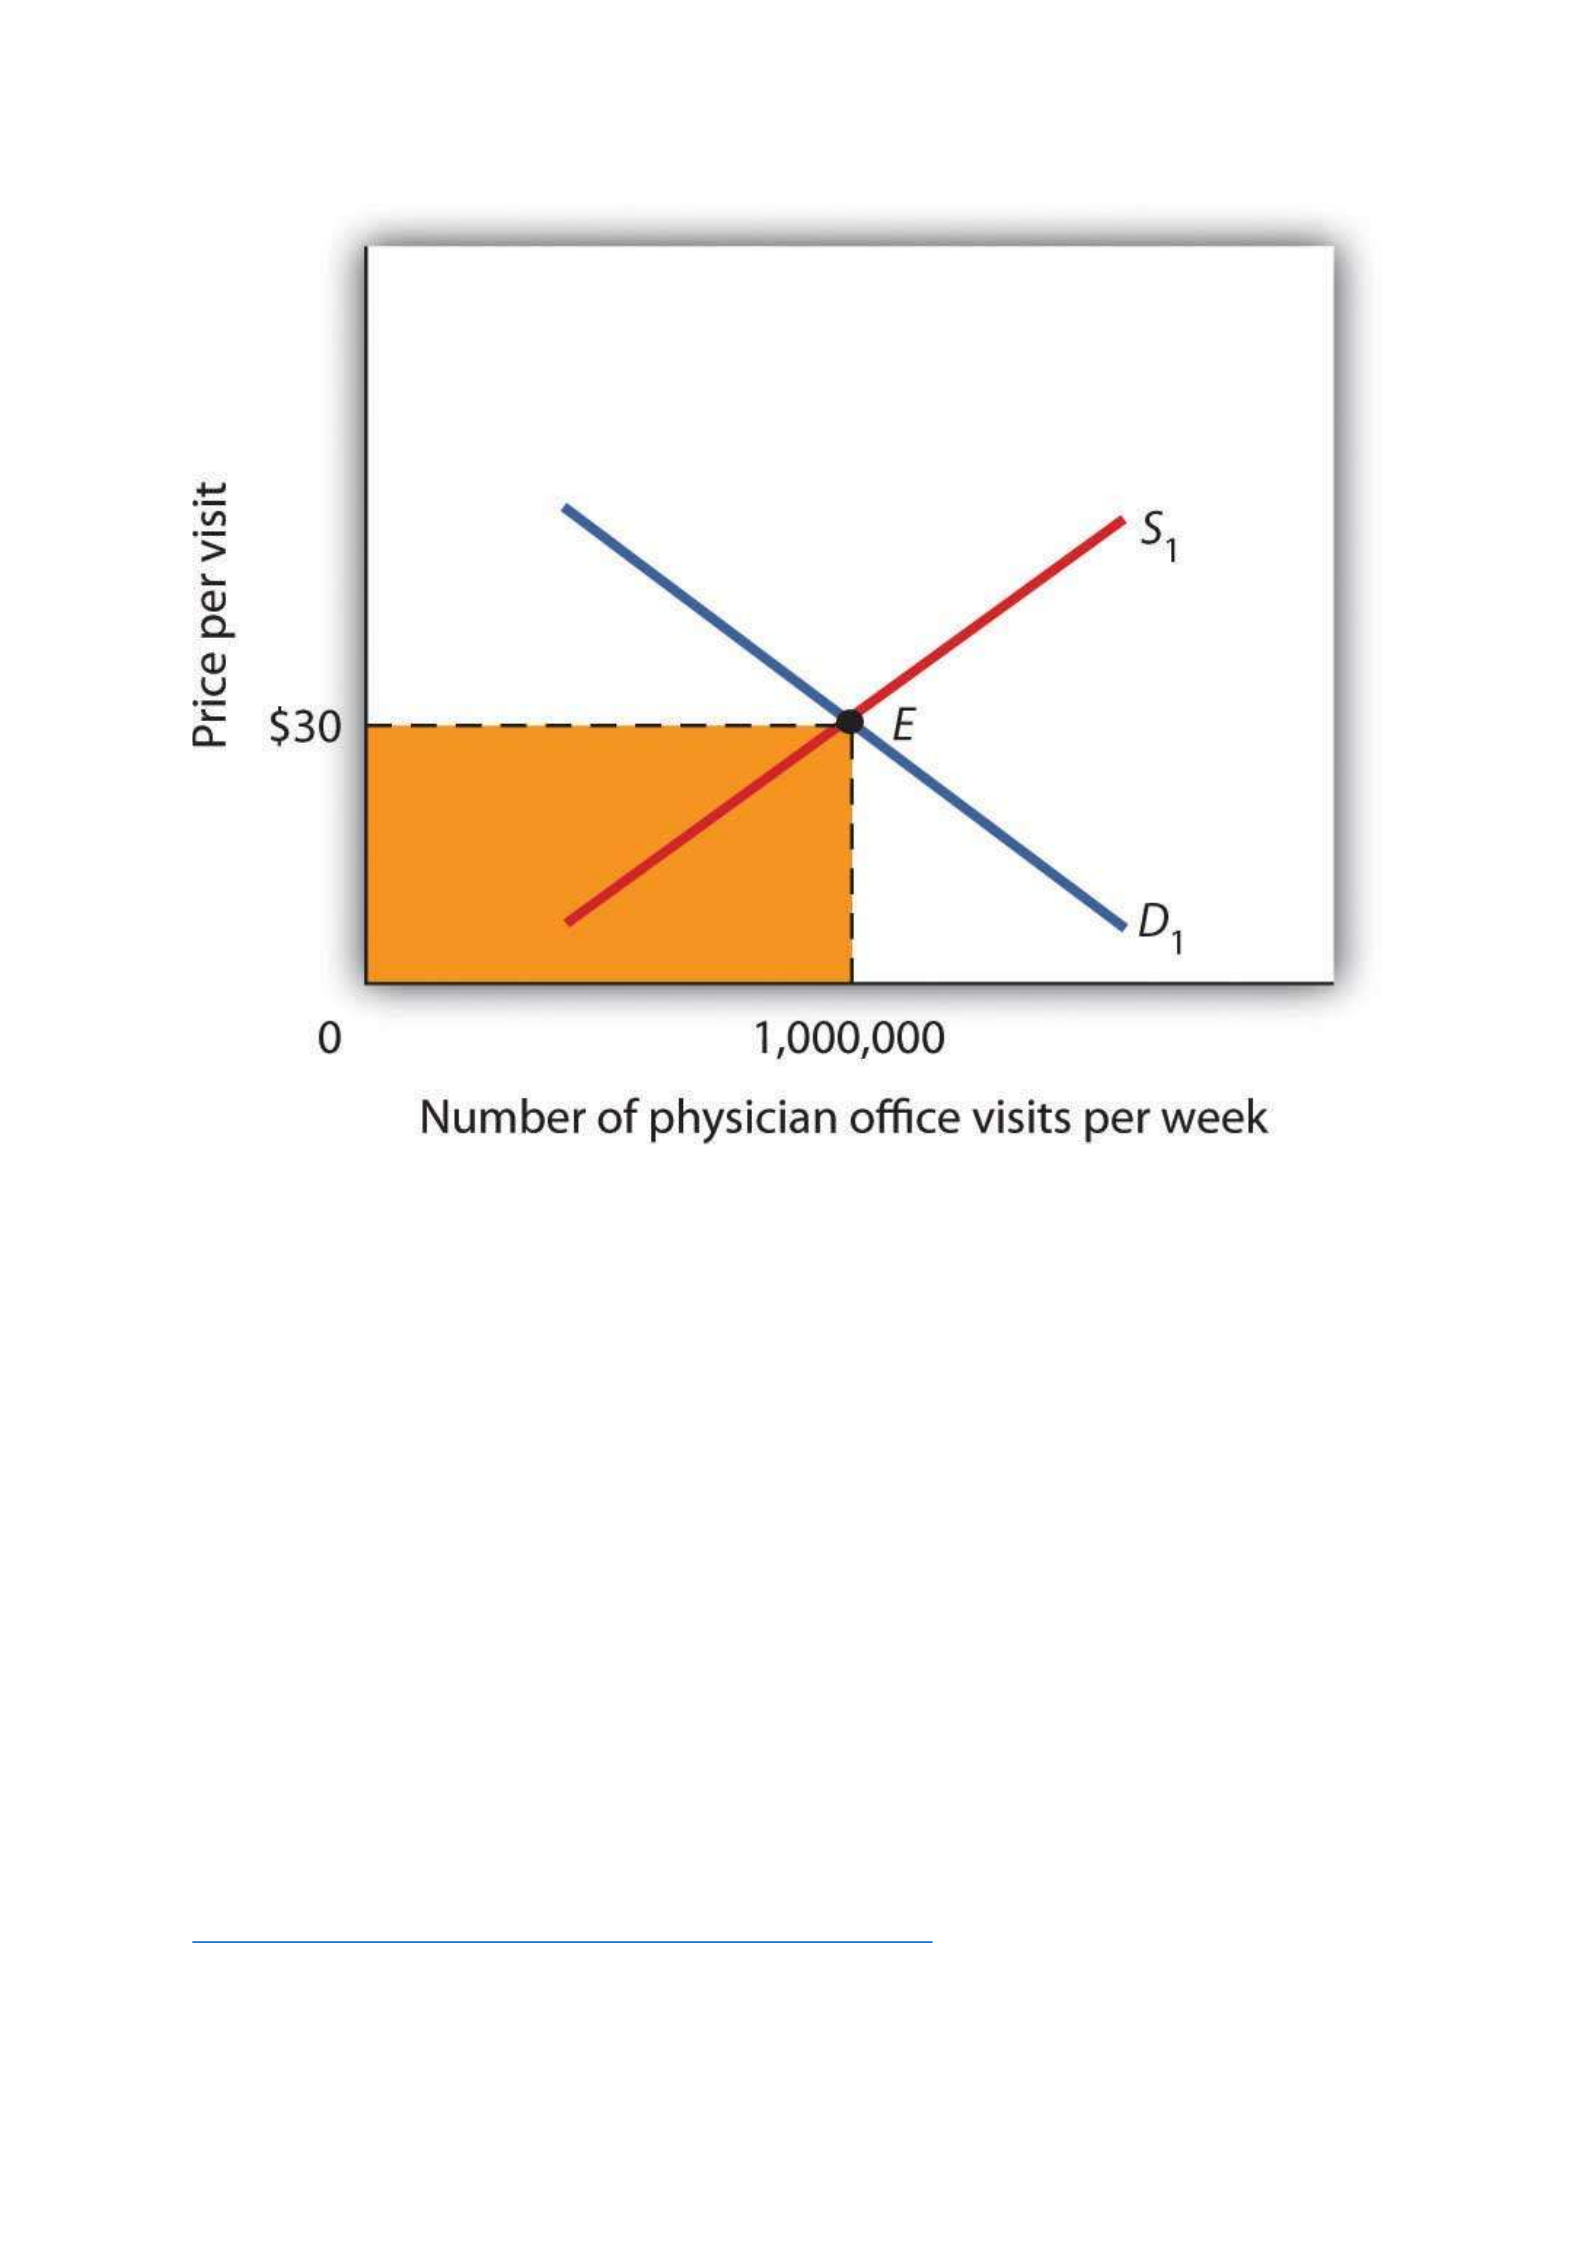
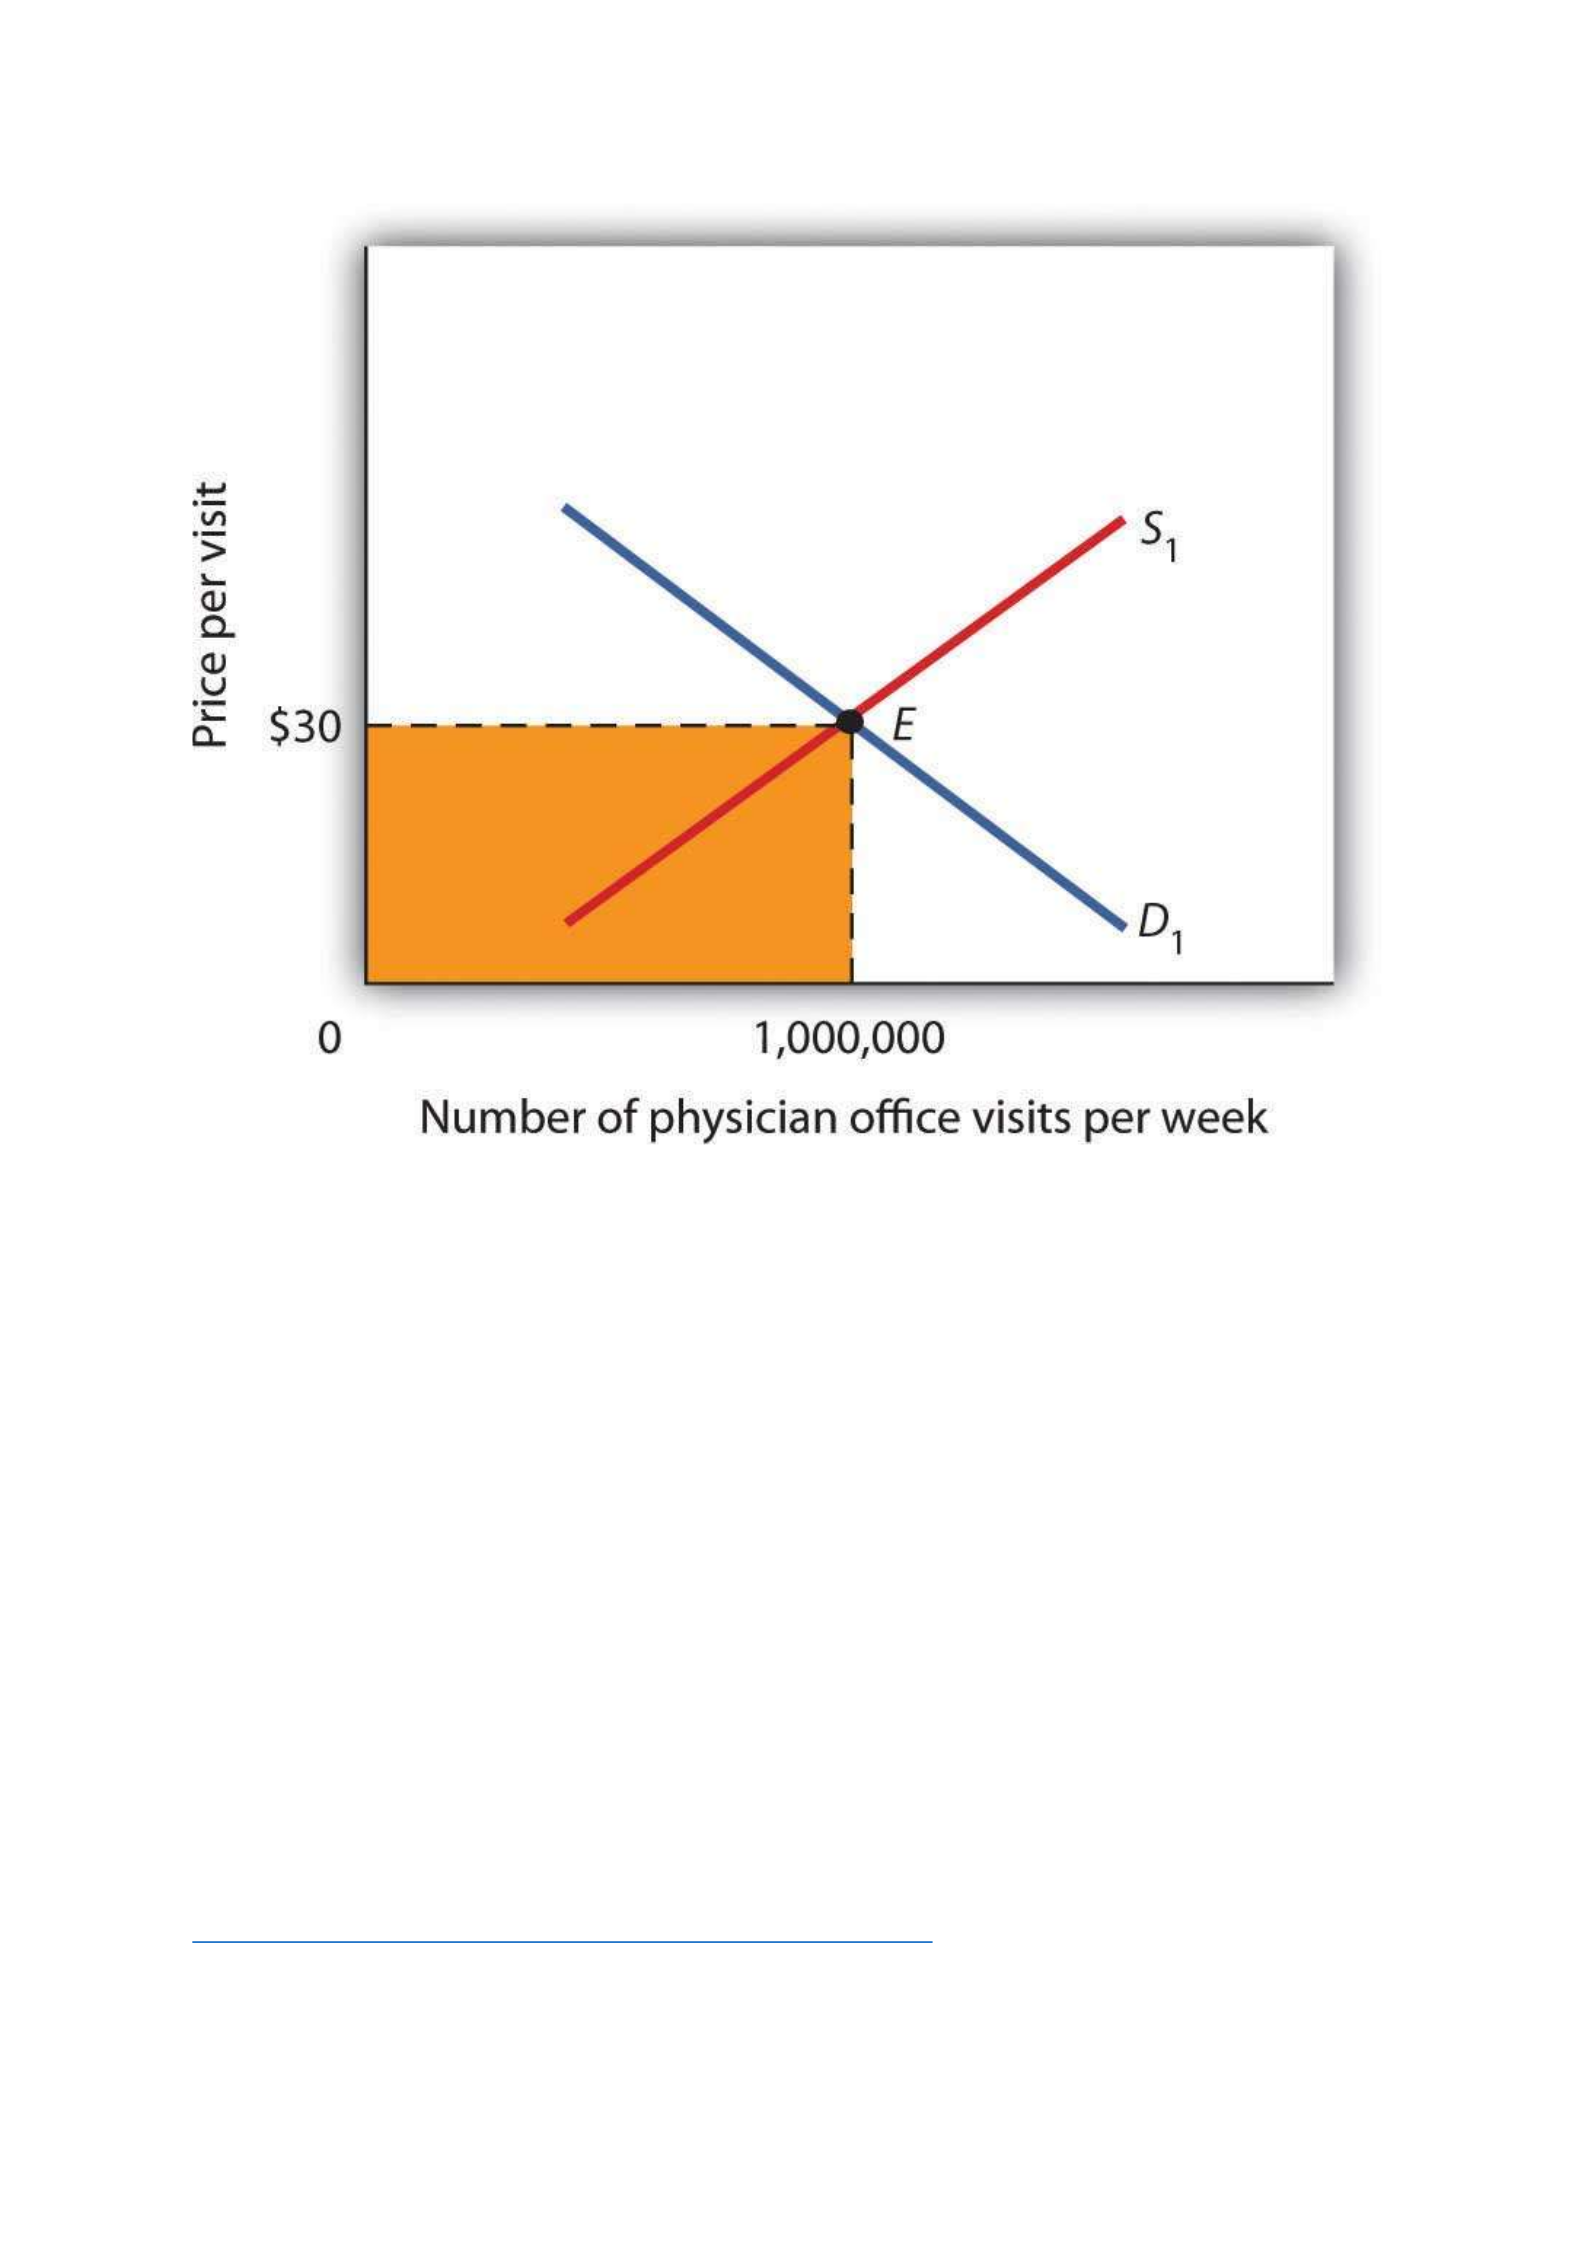
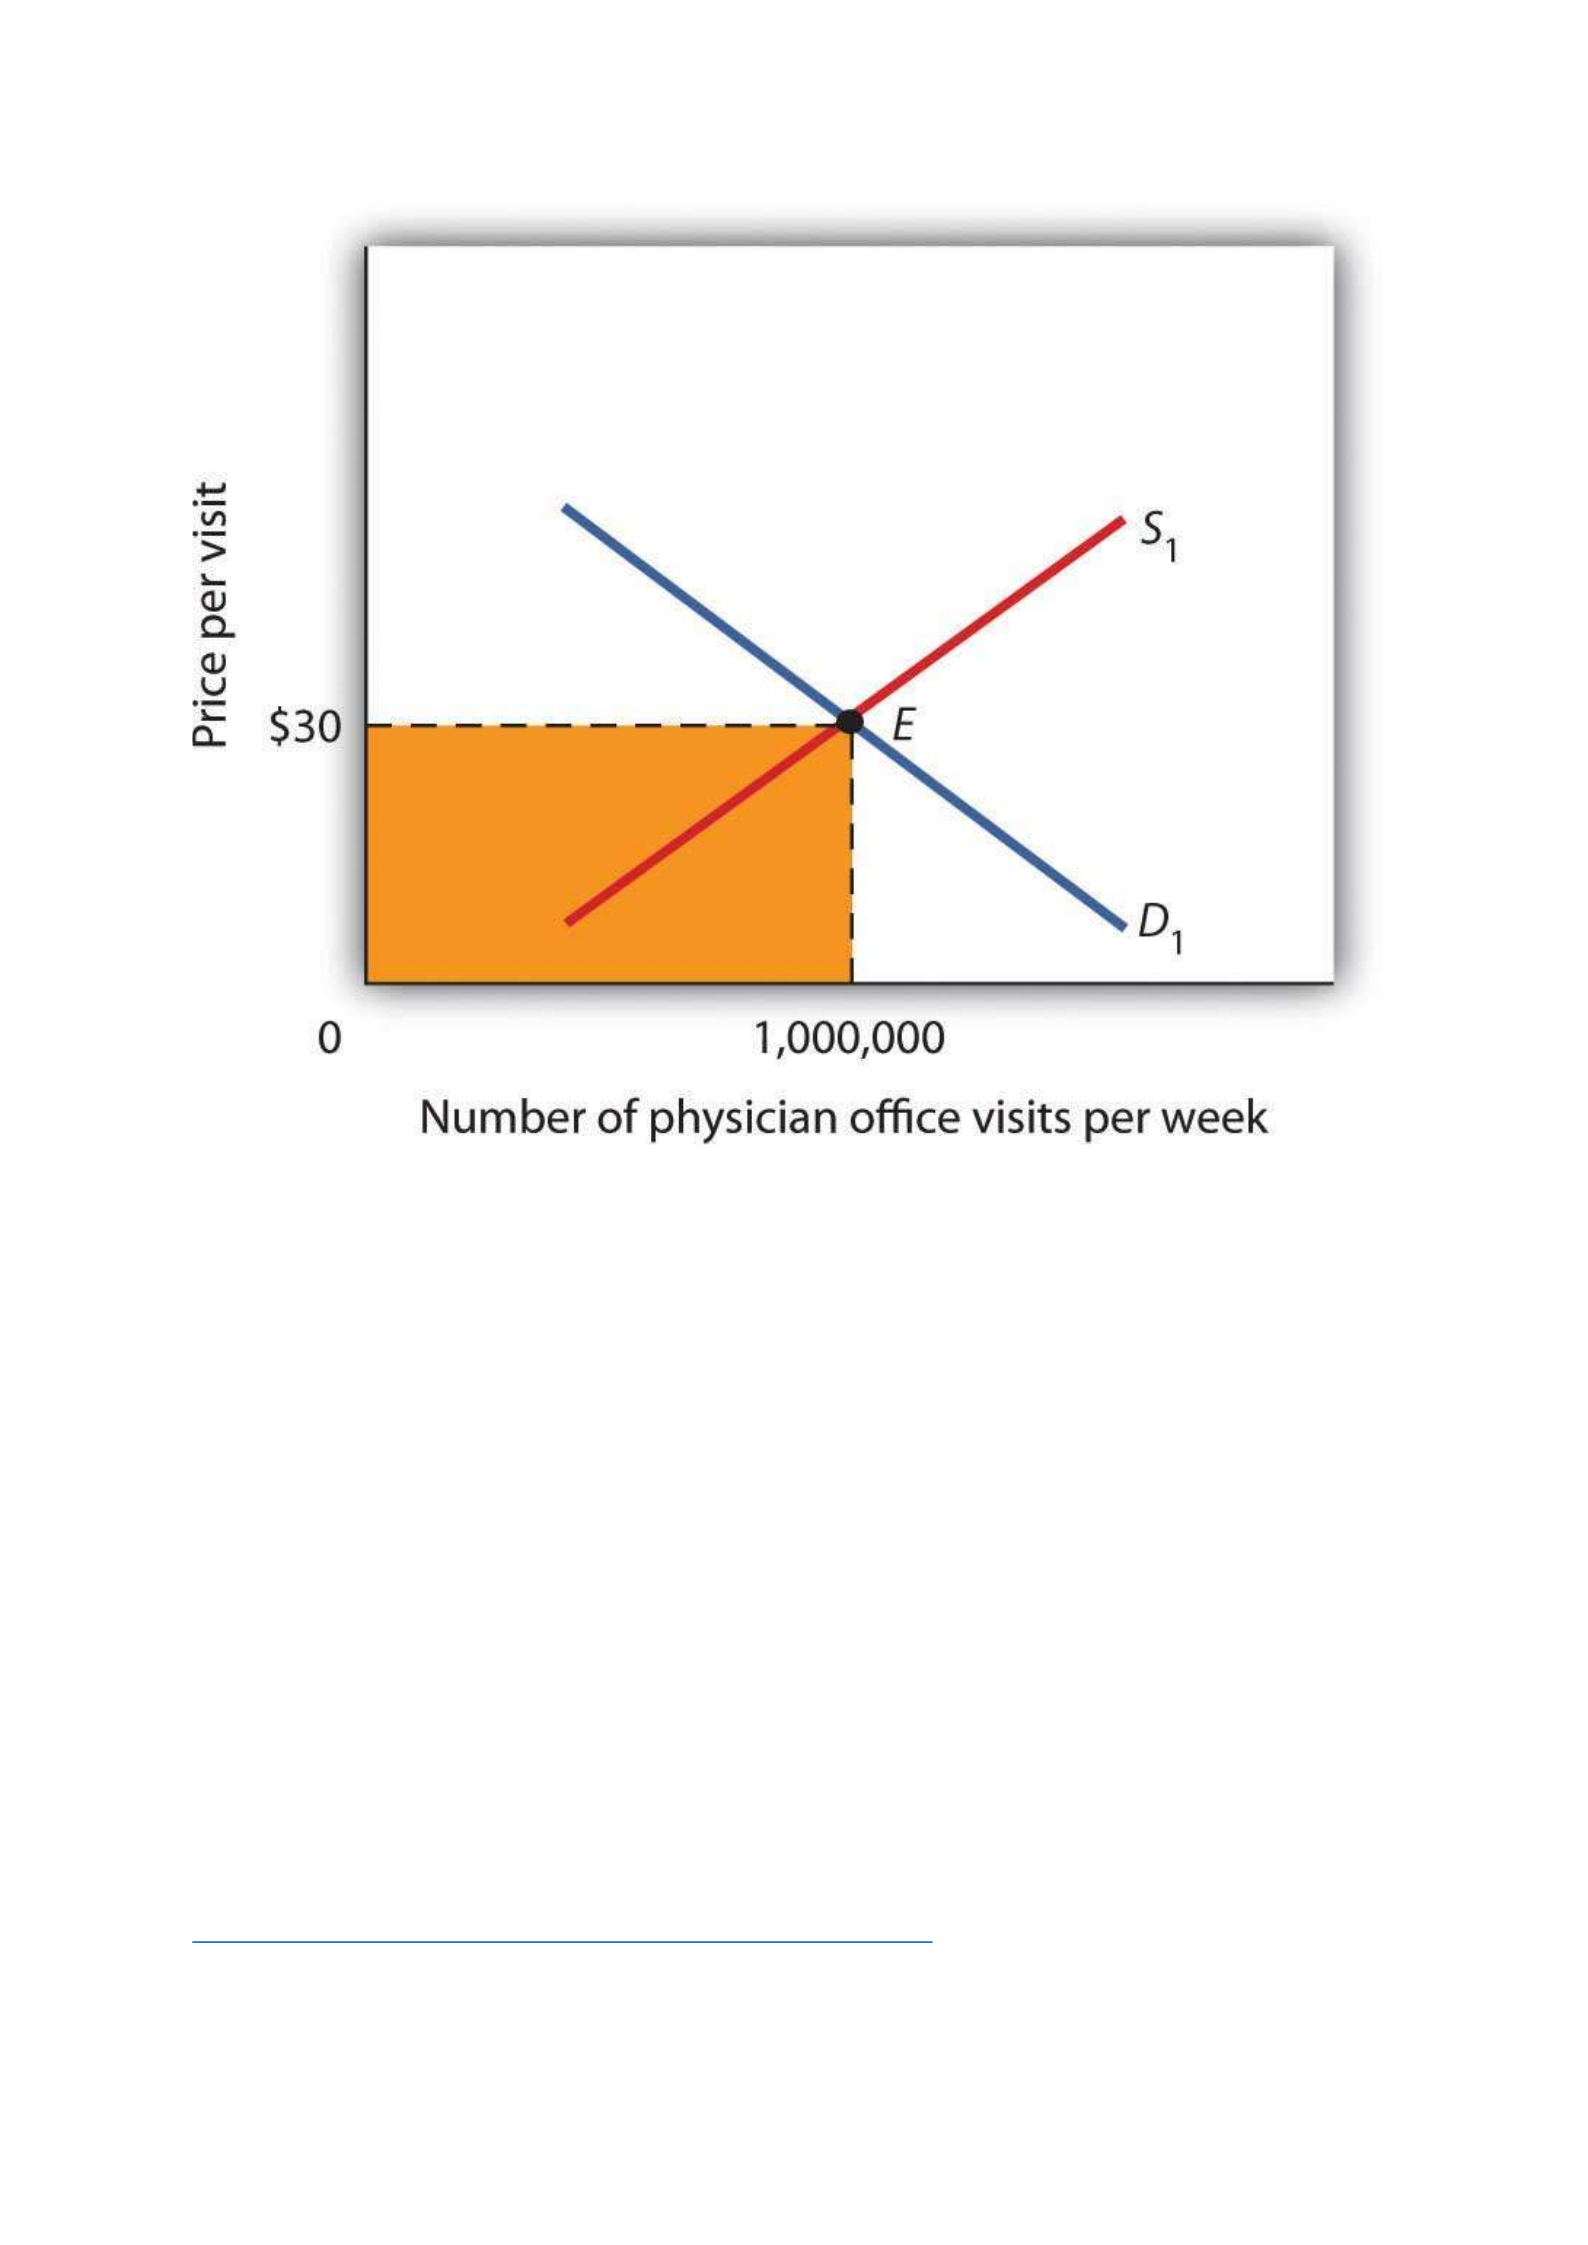
Figure 4.11 Total Spending for Physician Office Visits
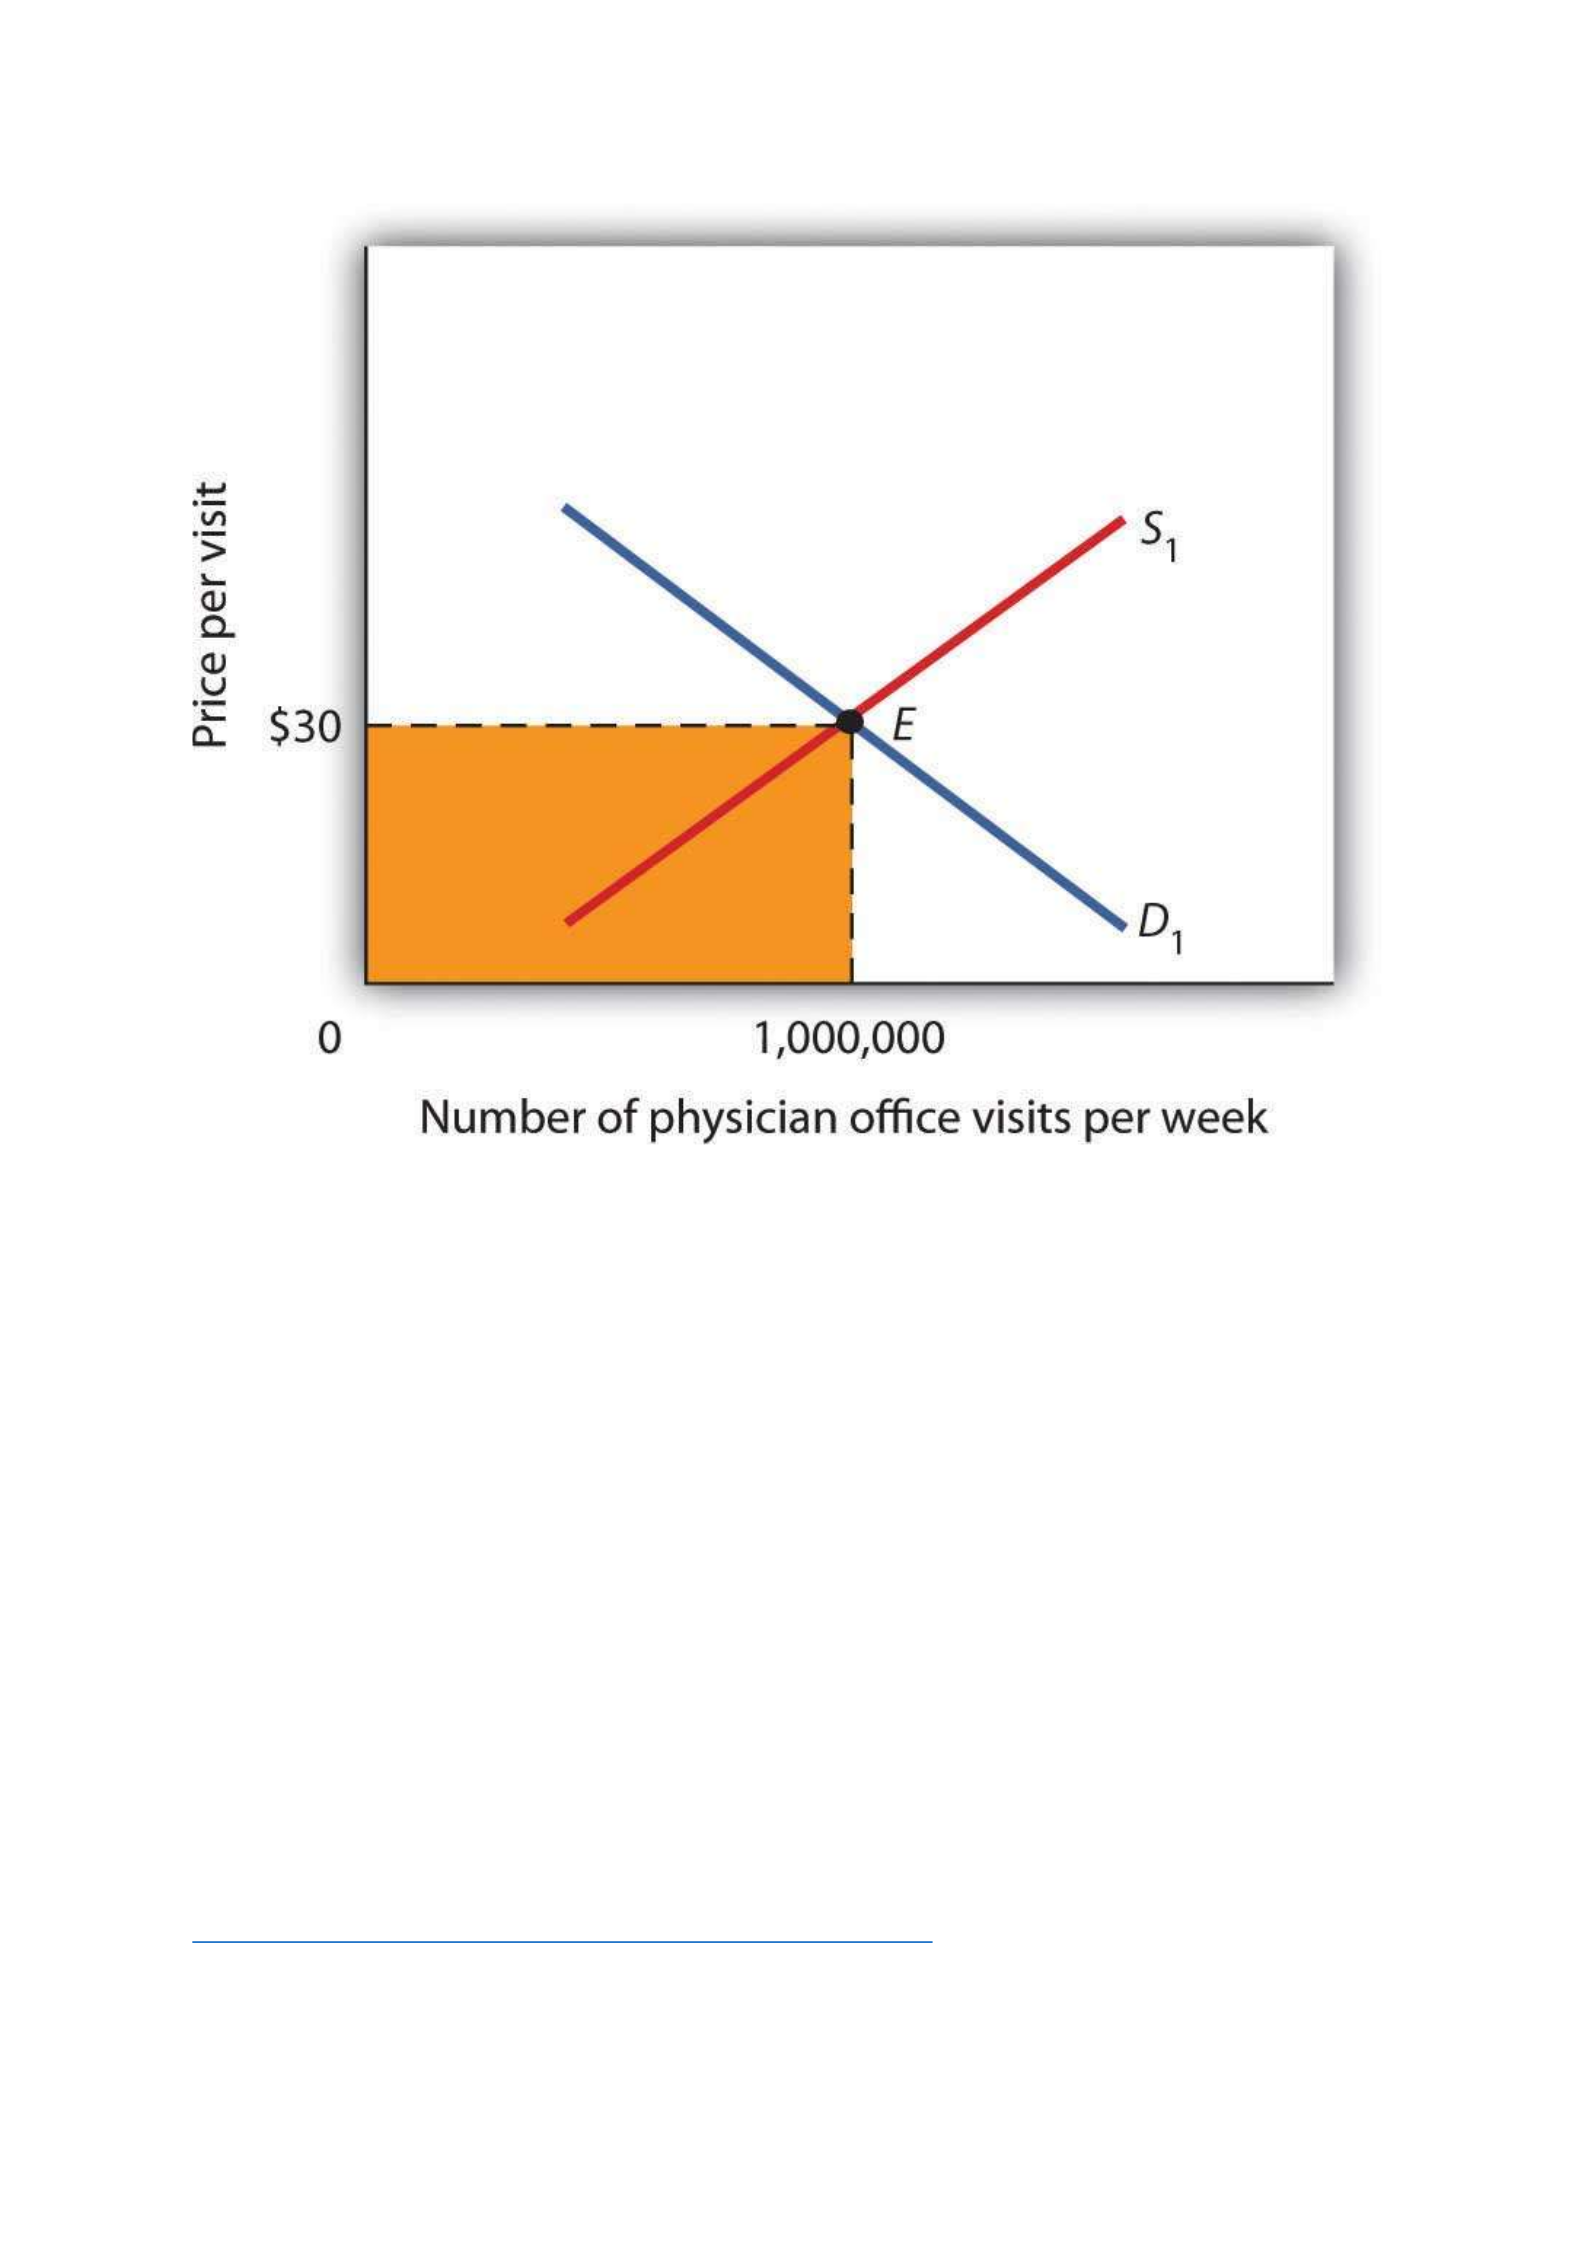
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
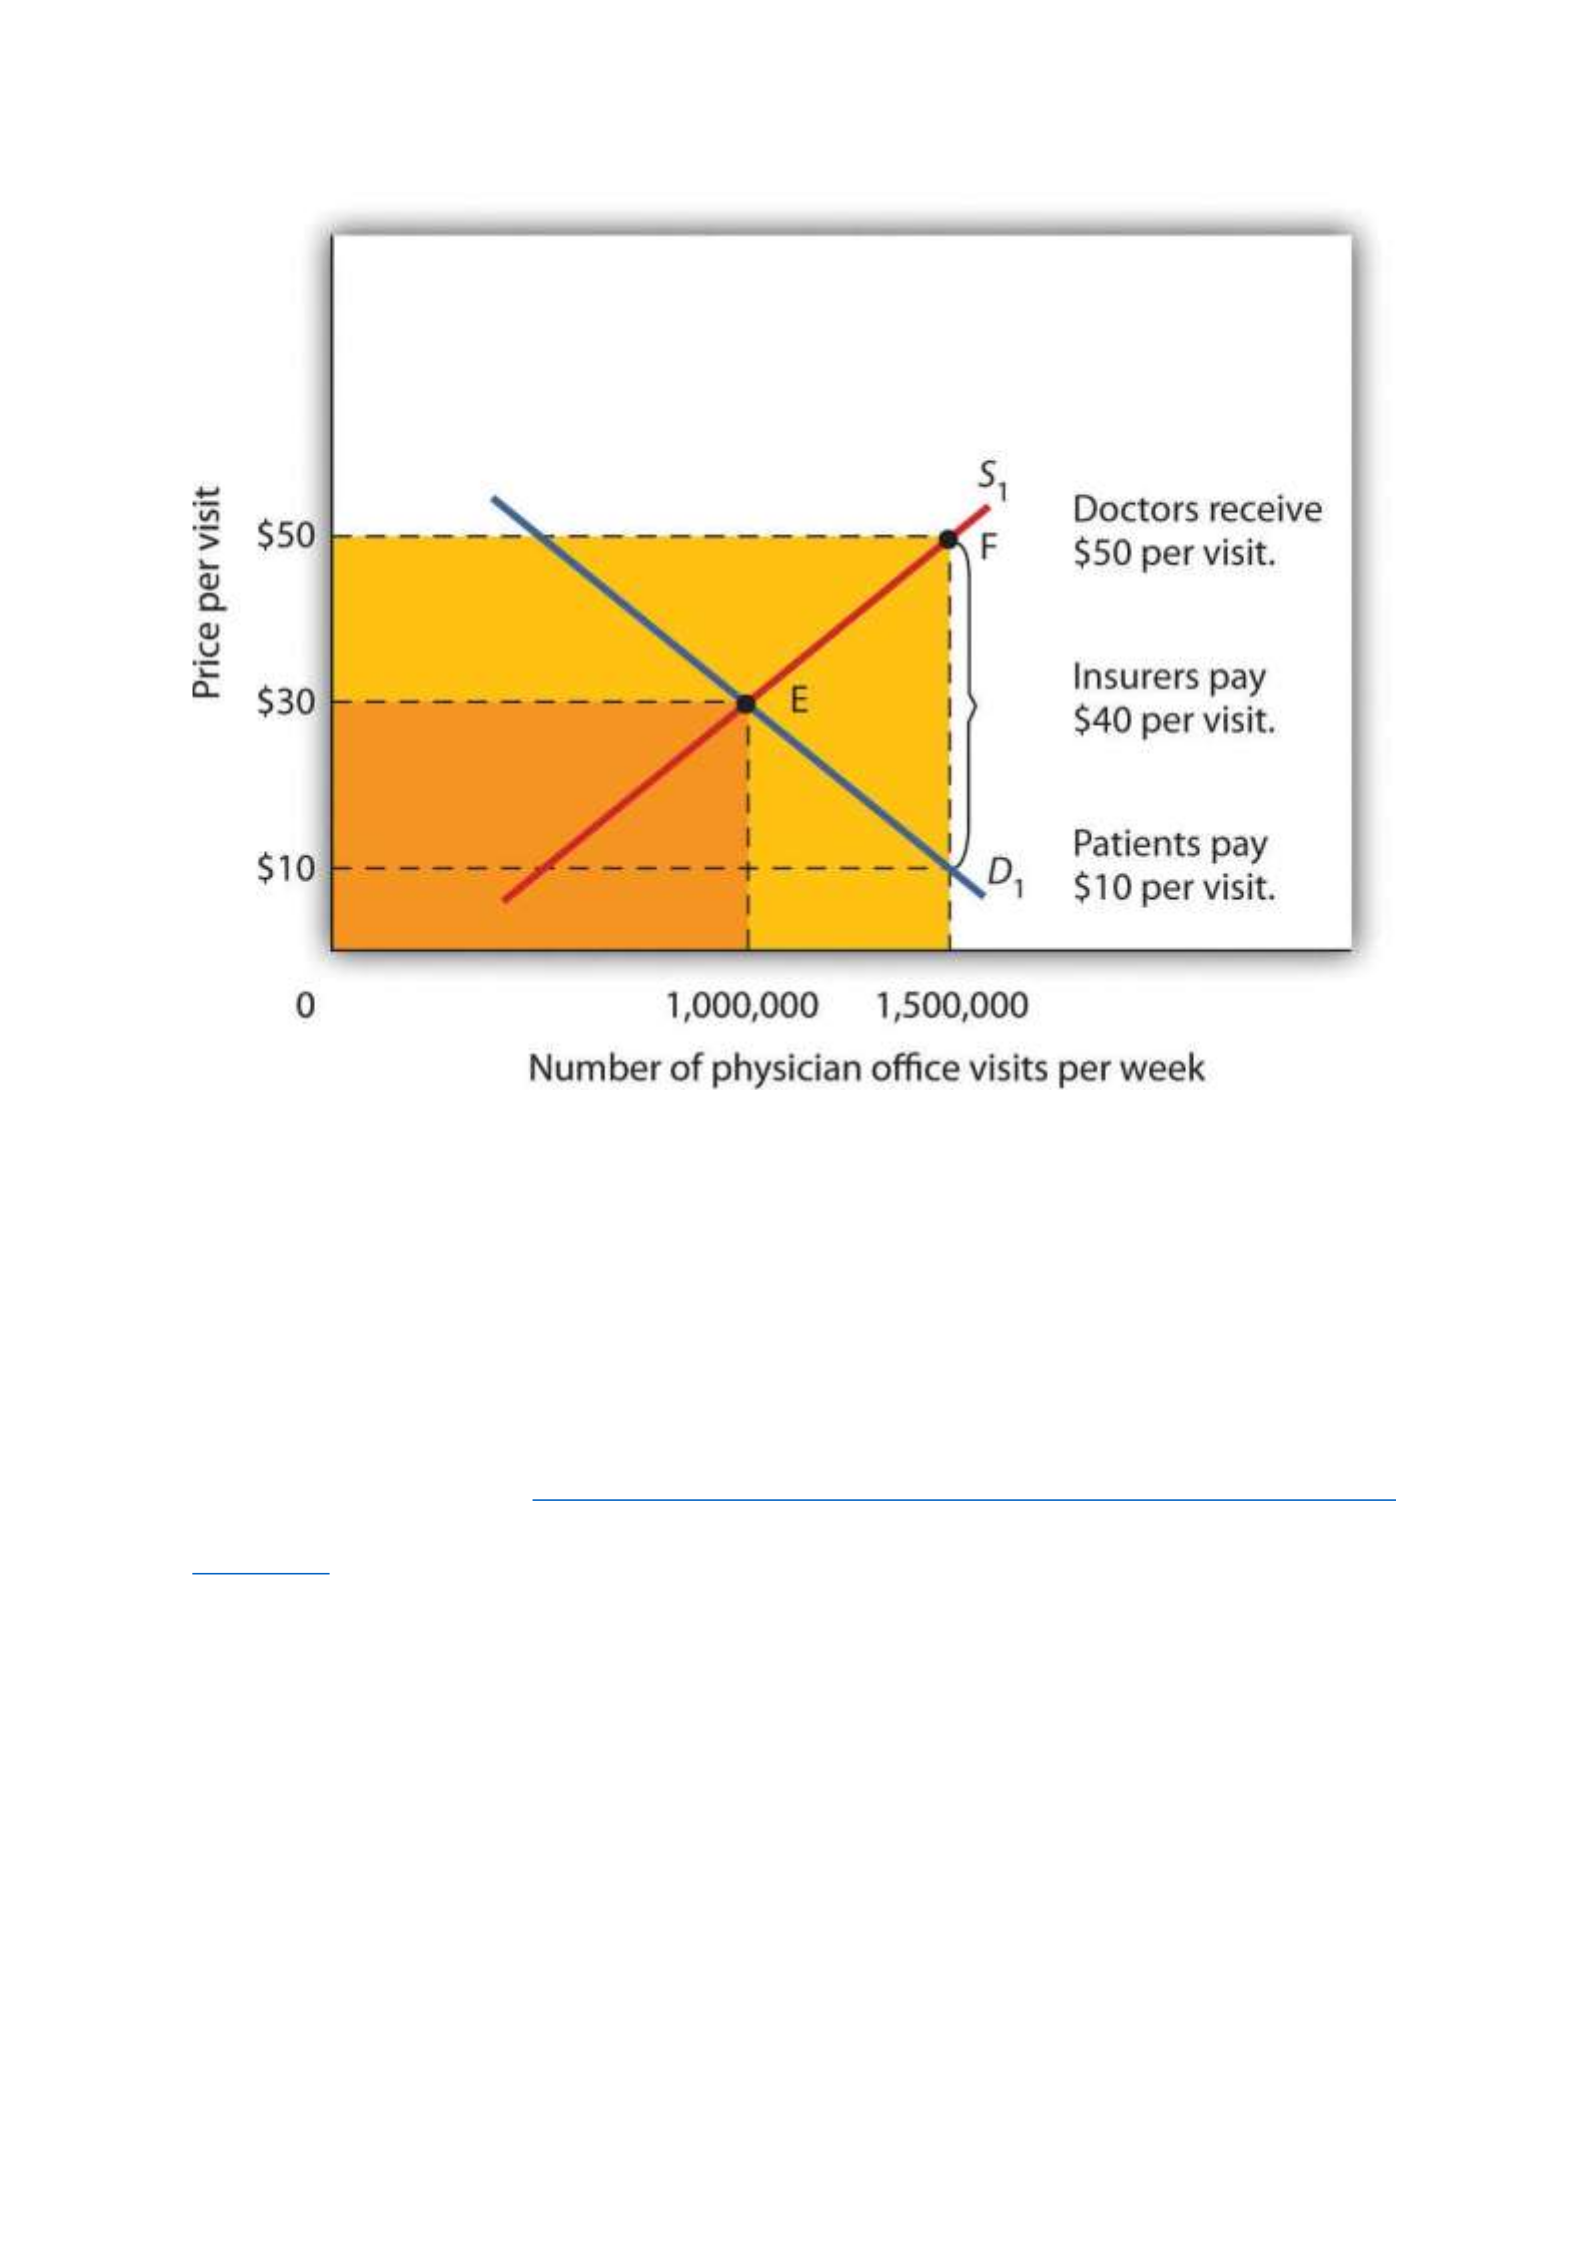
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

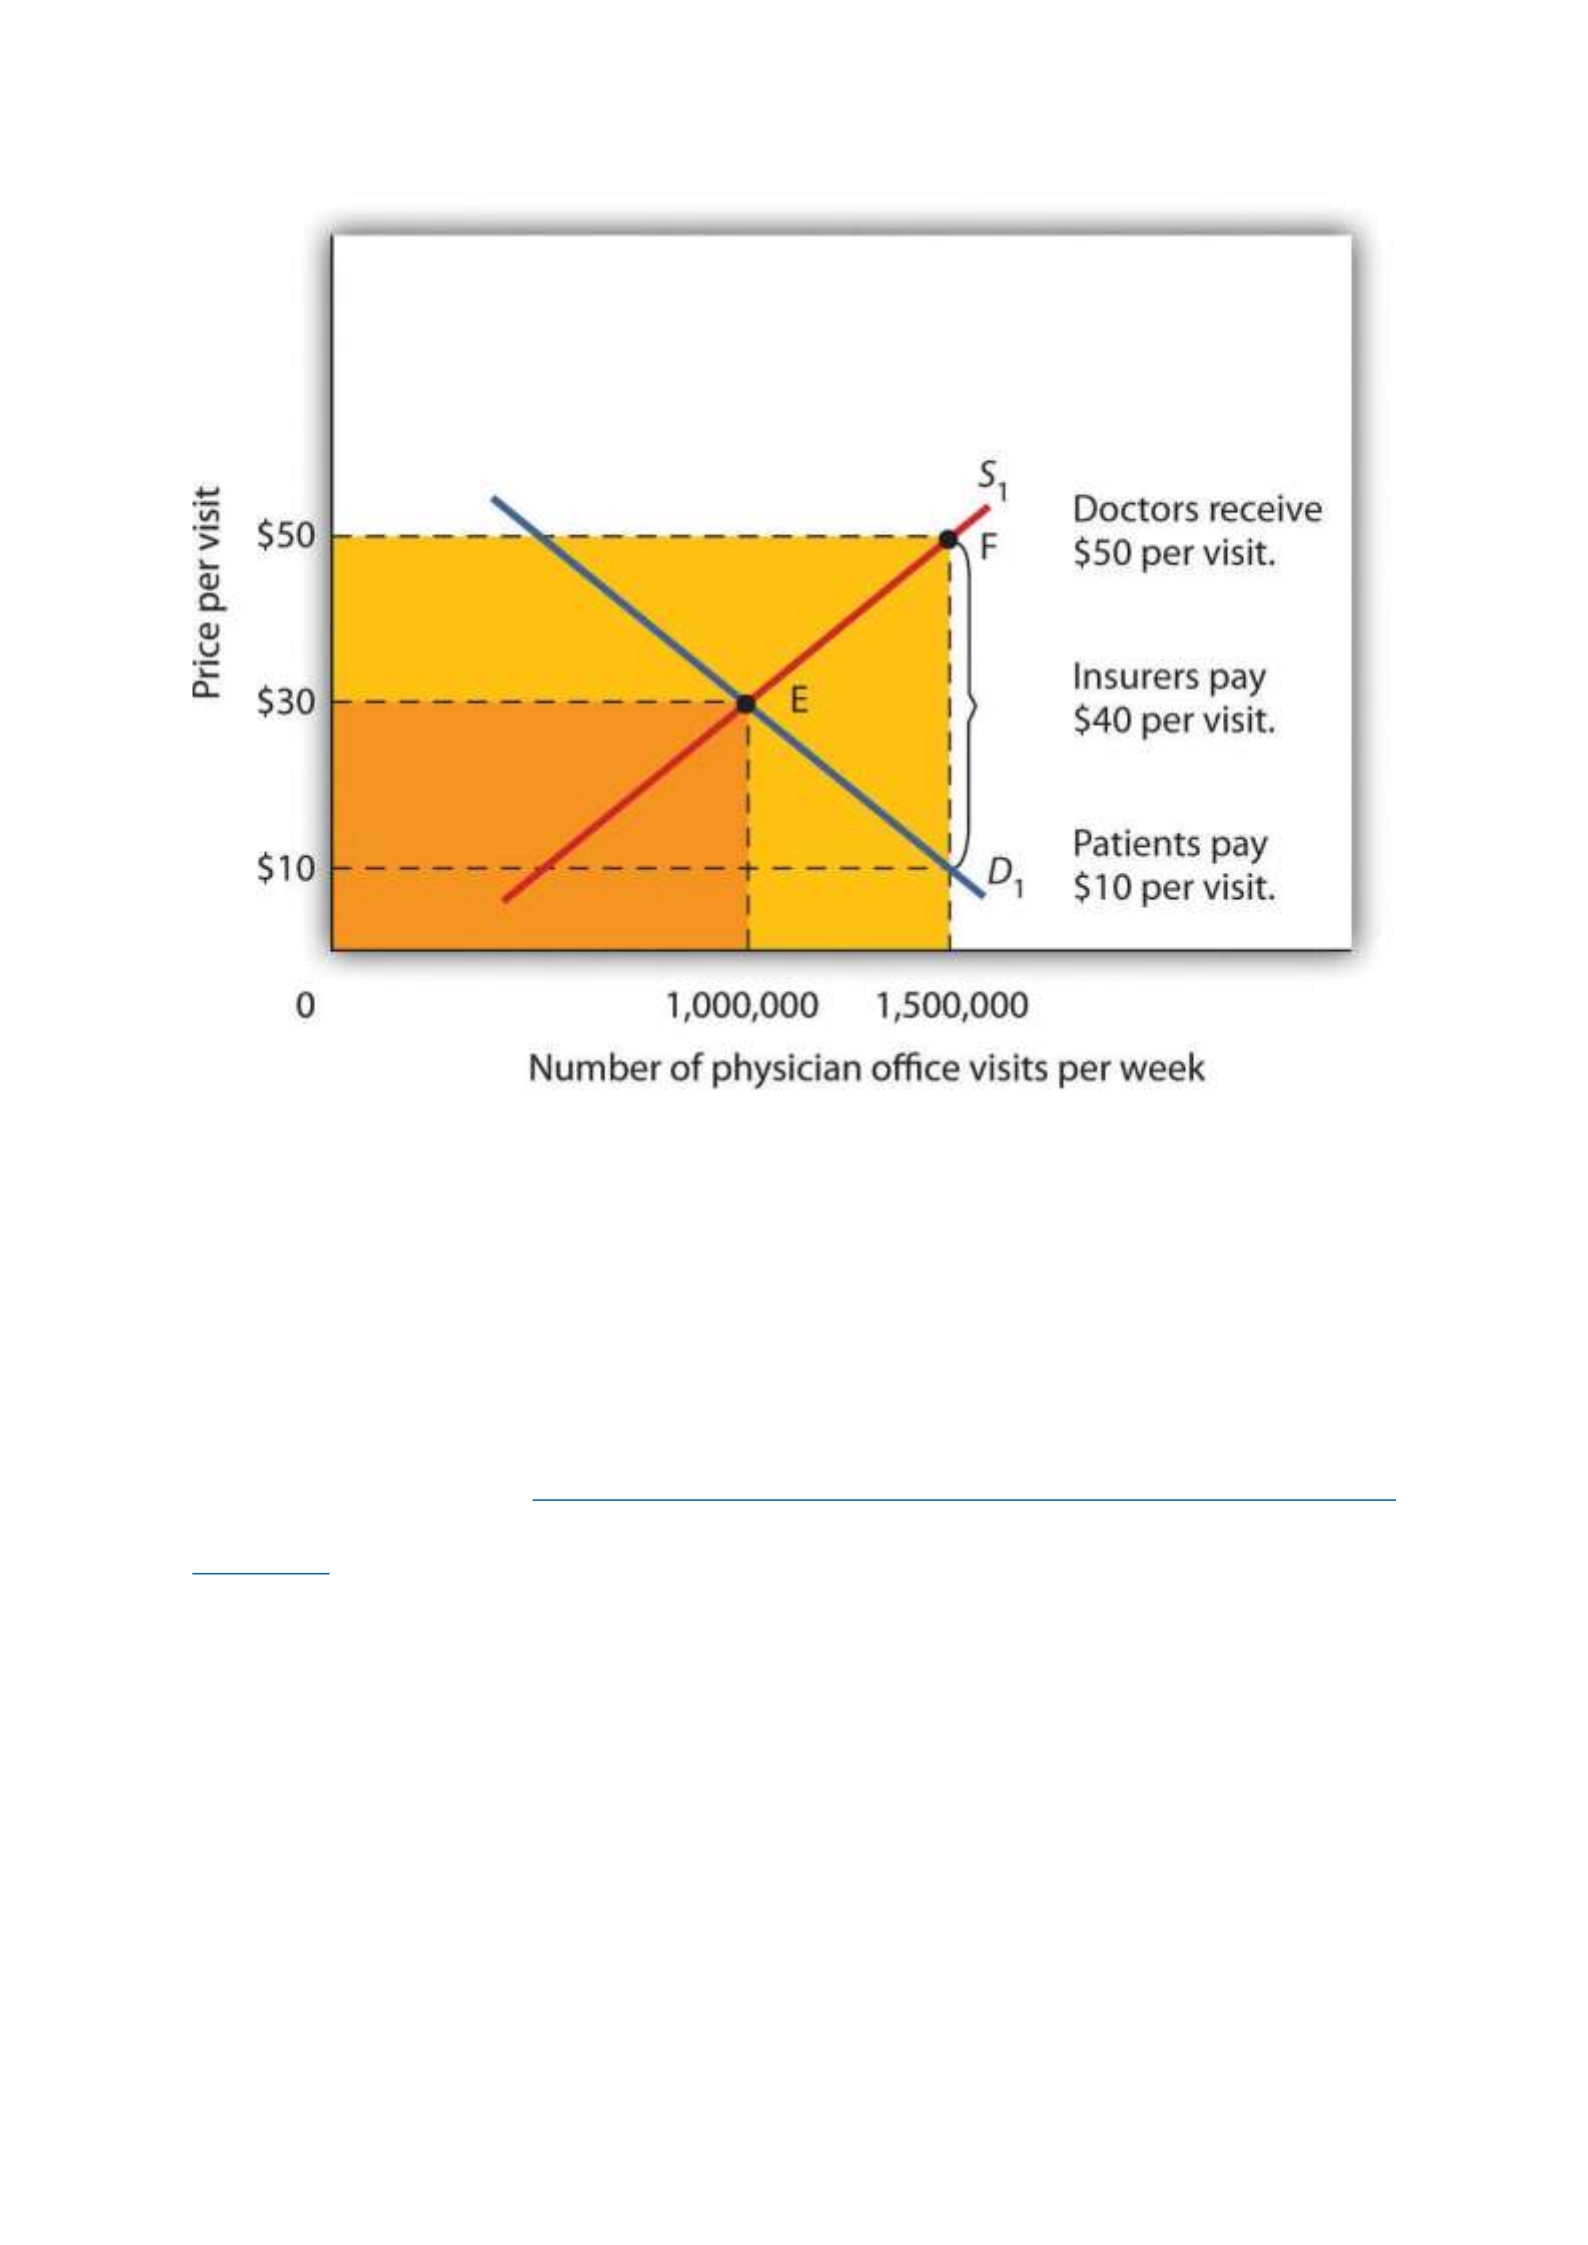
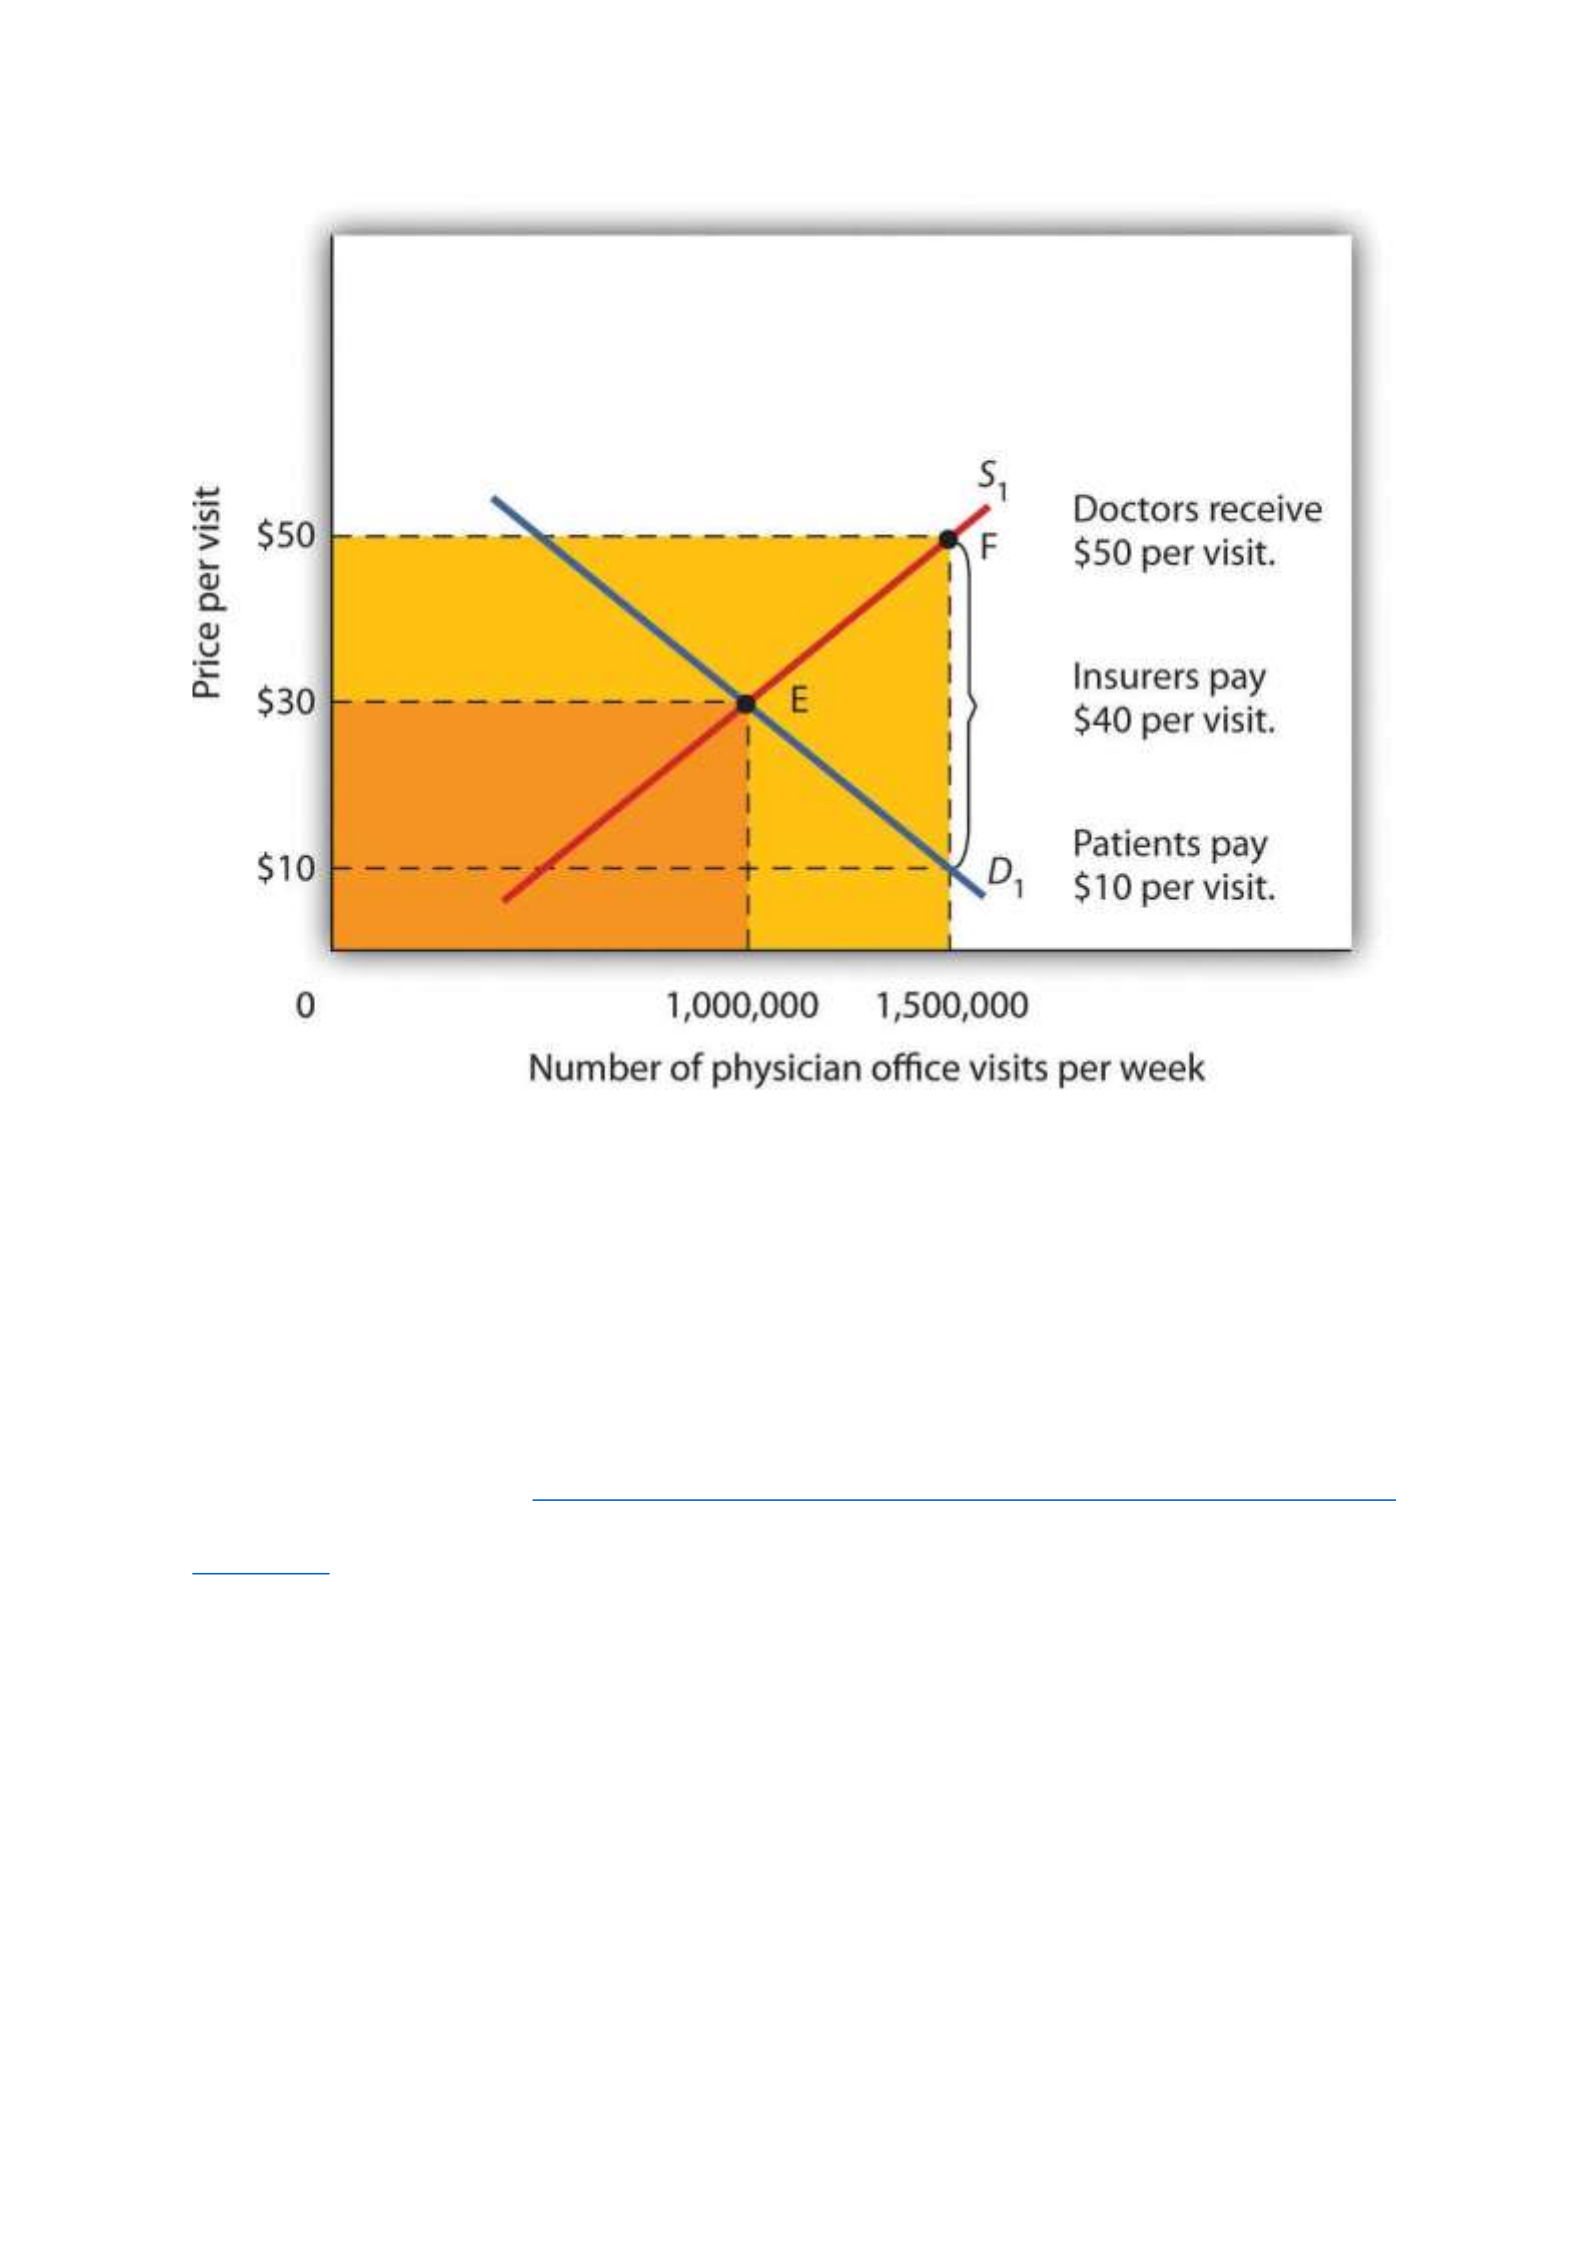
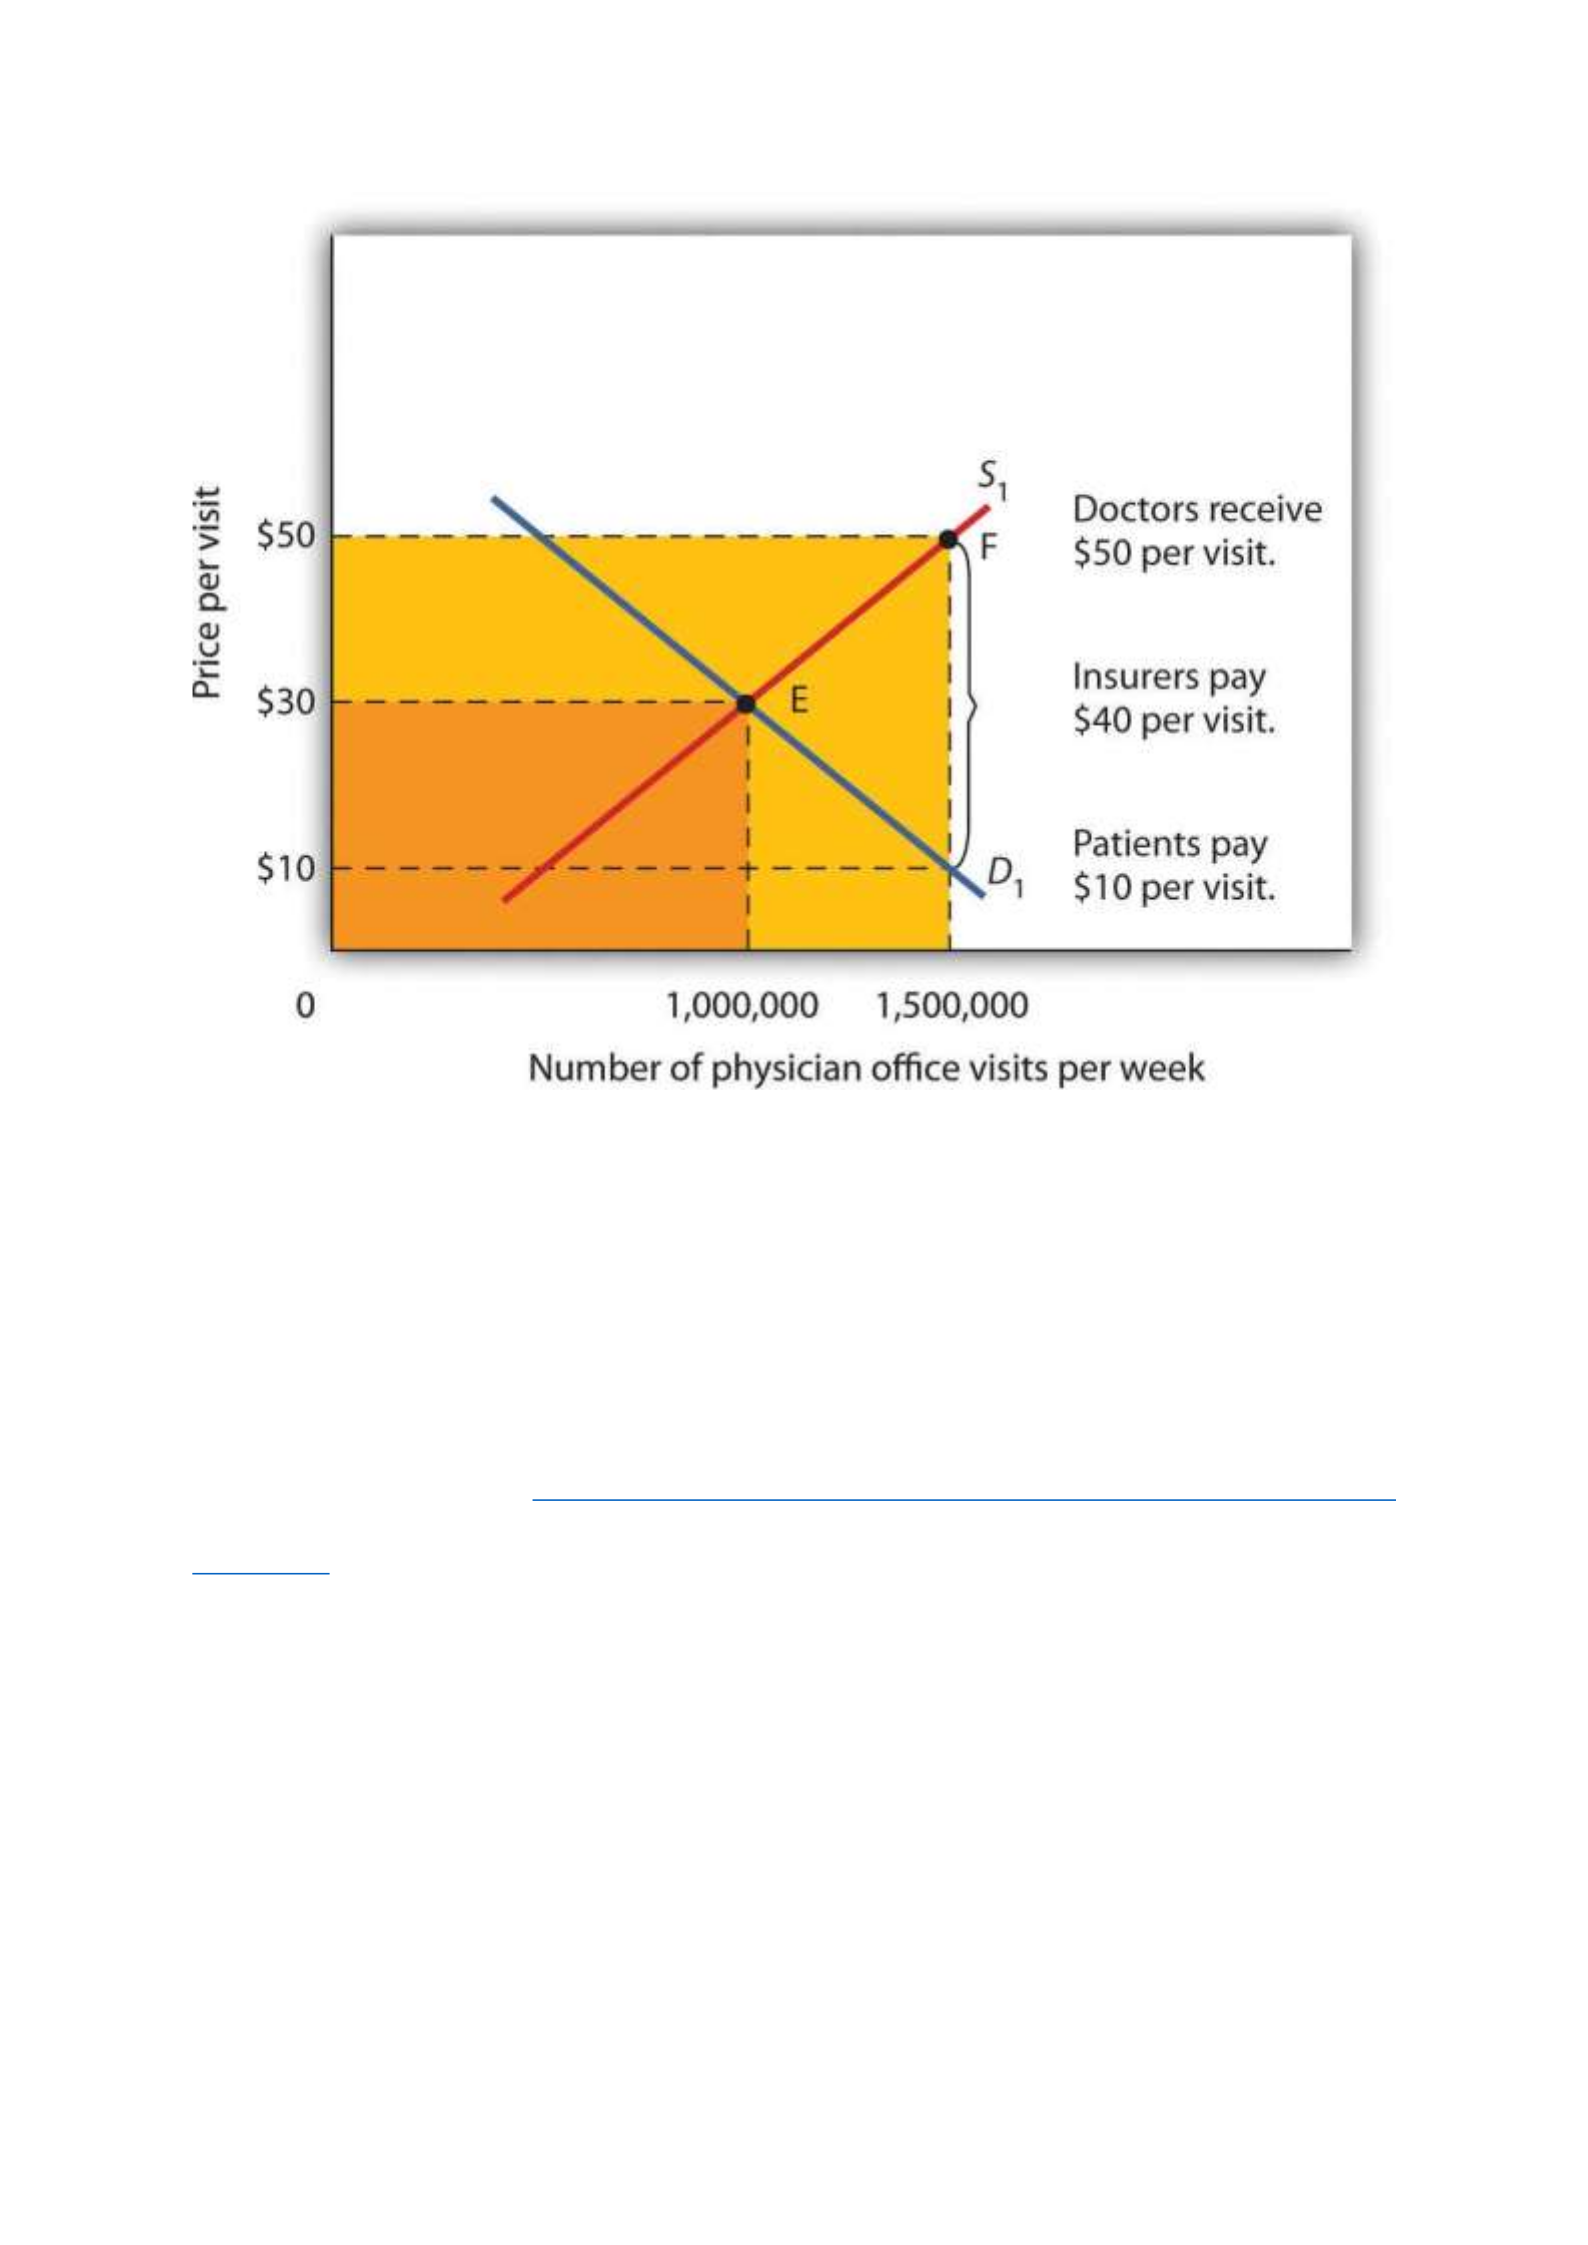
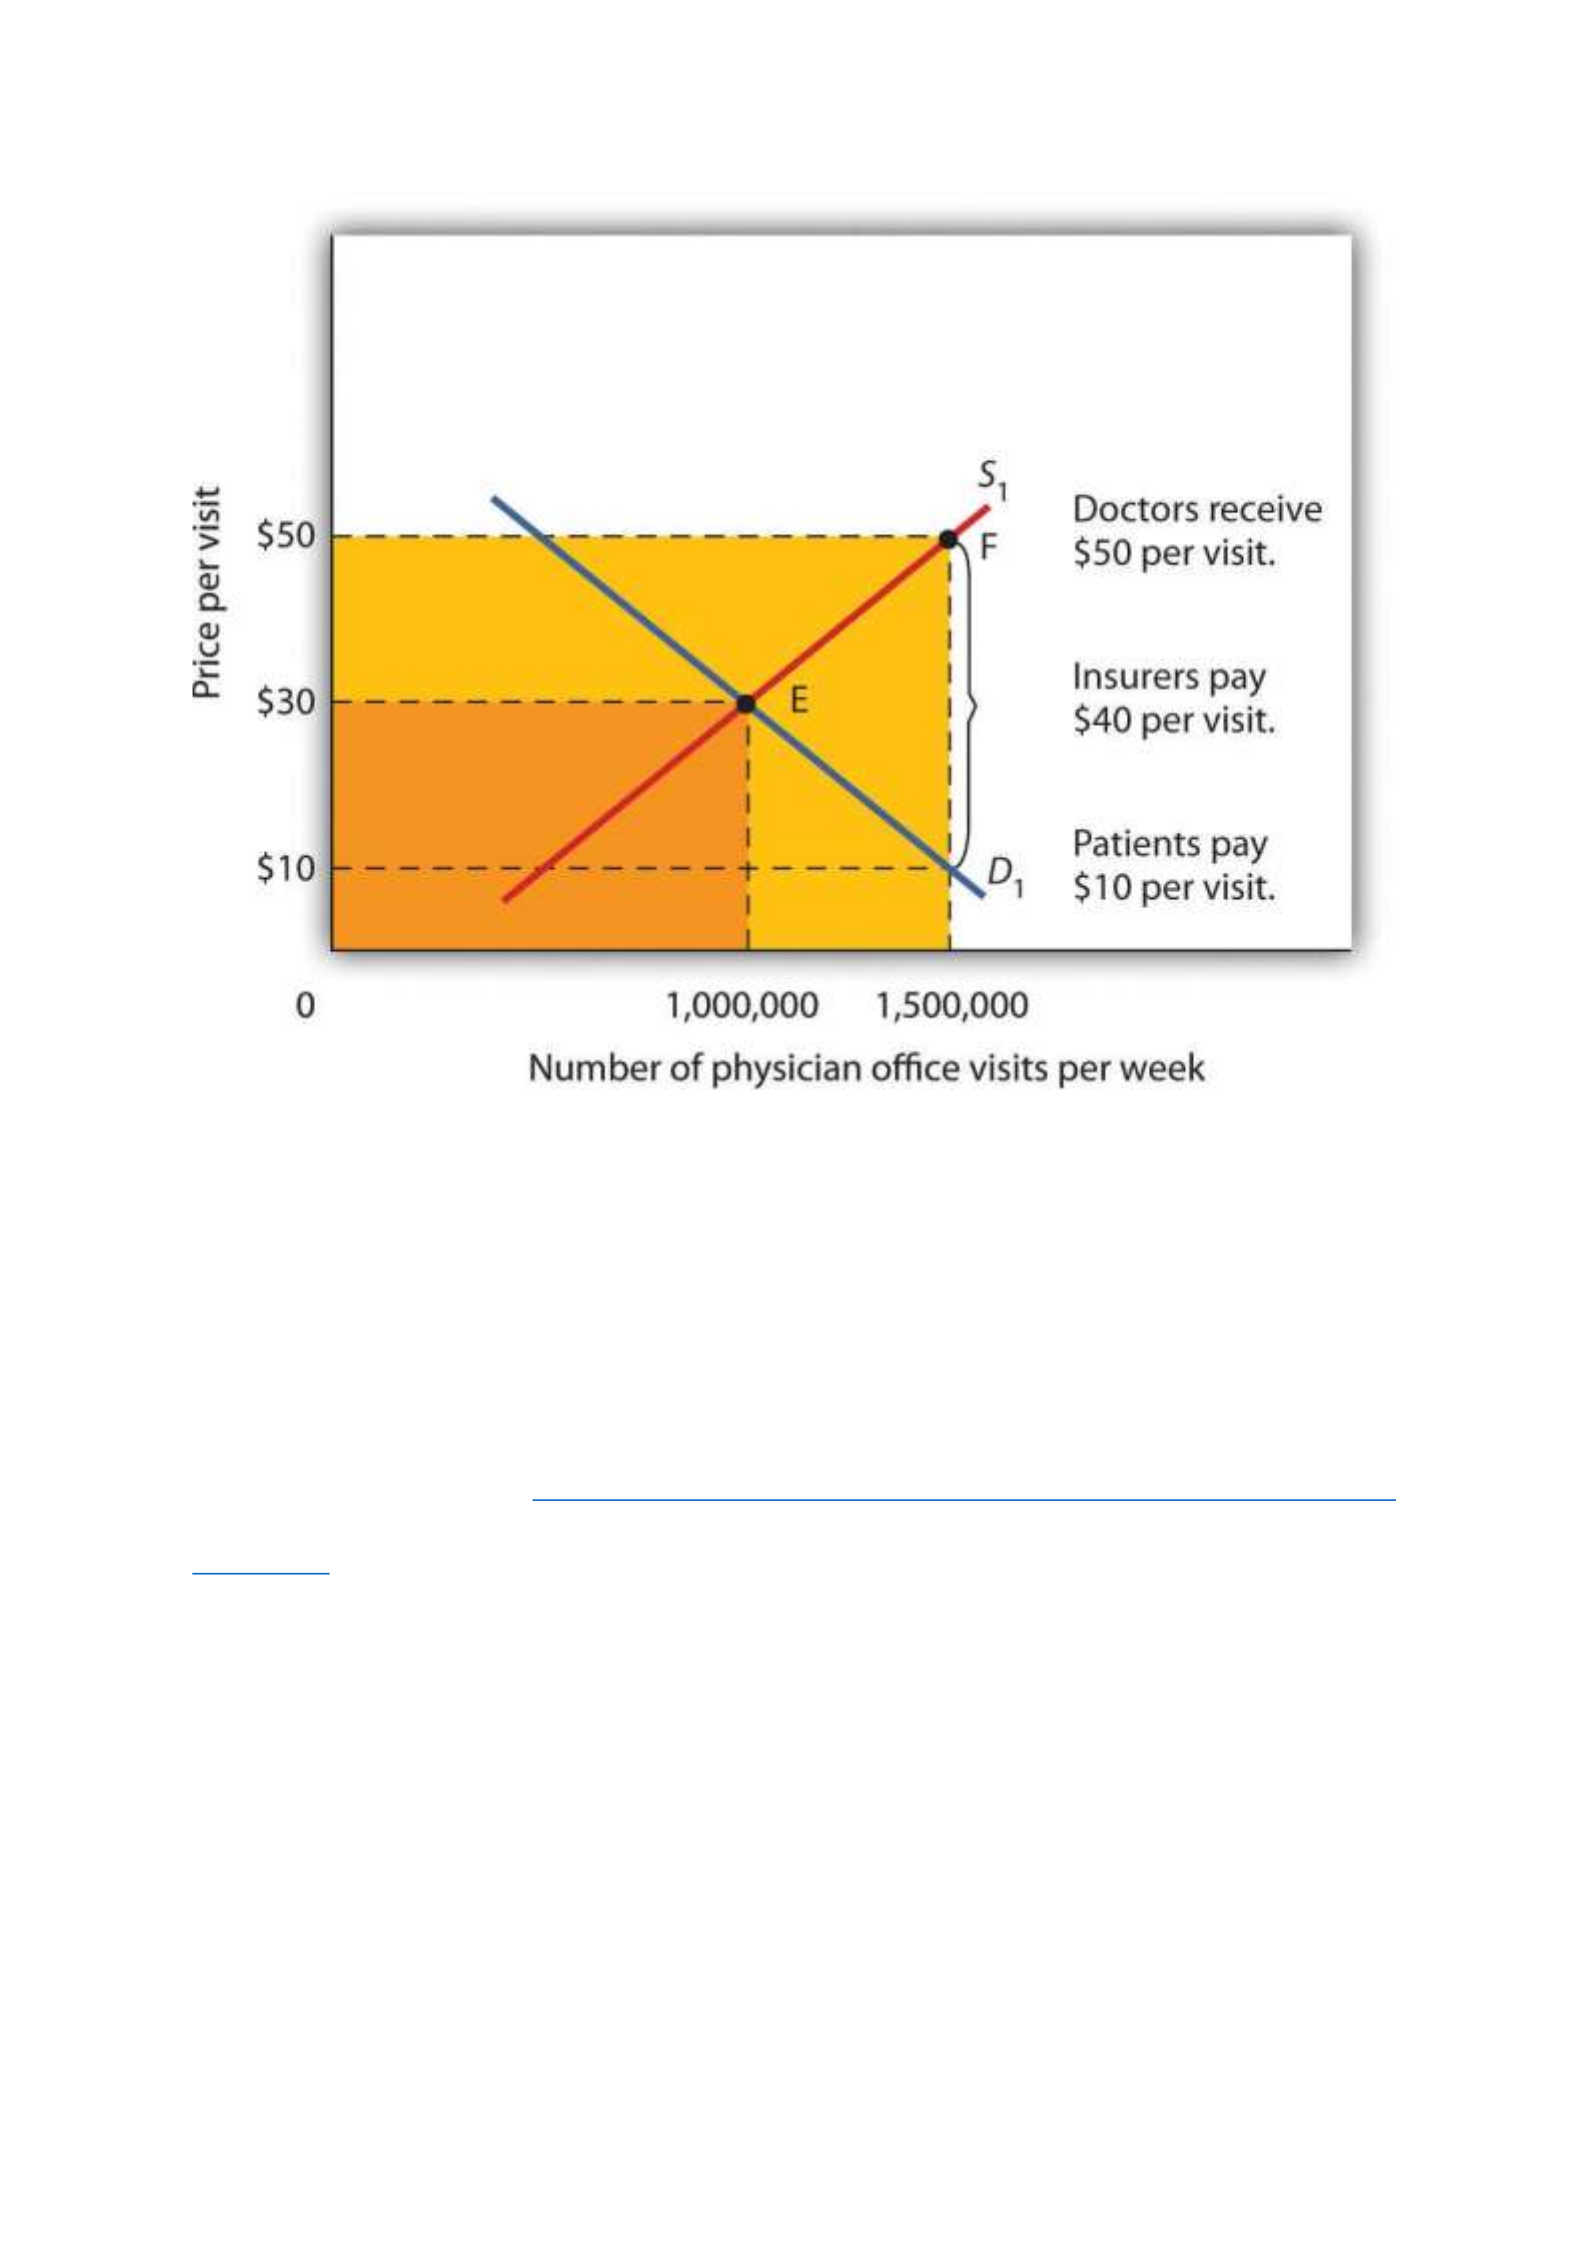
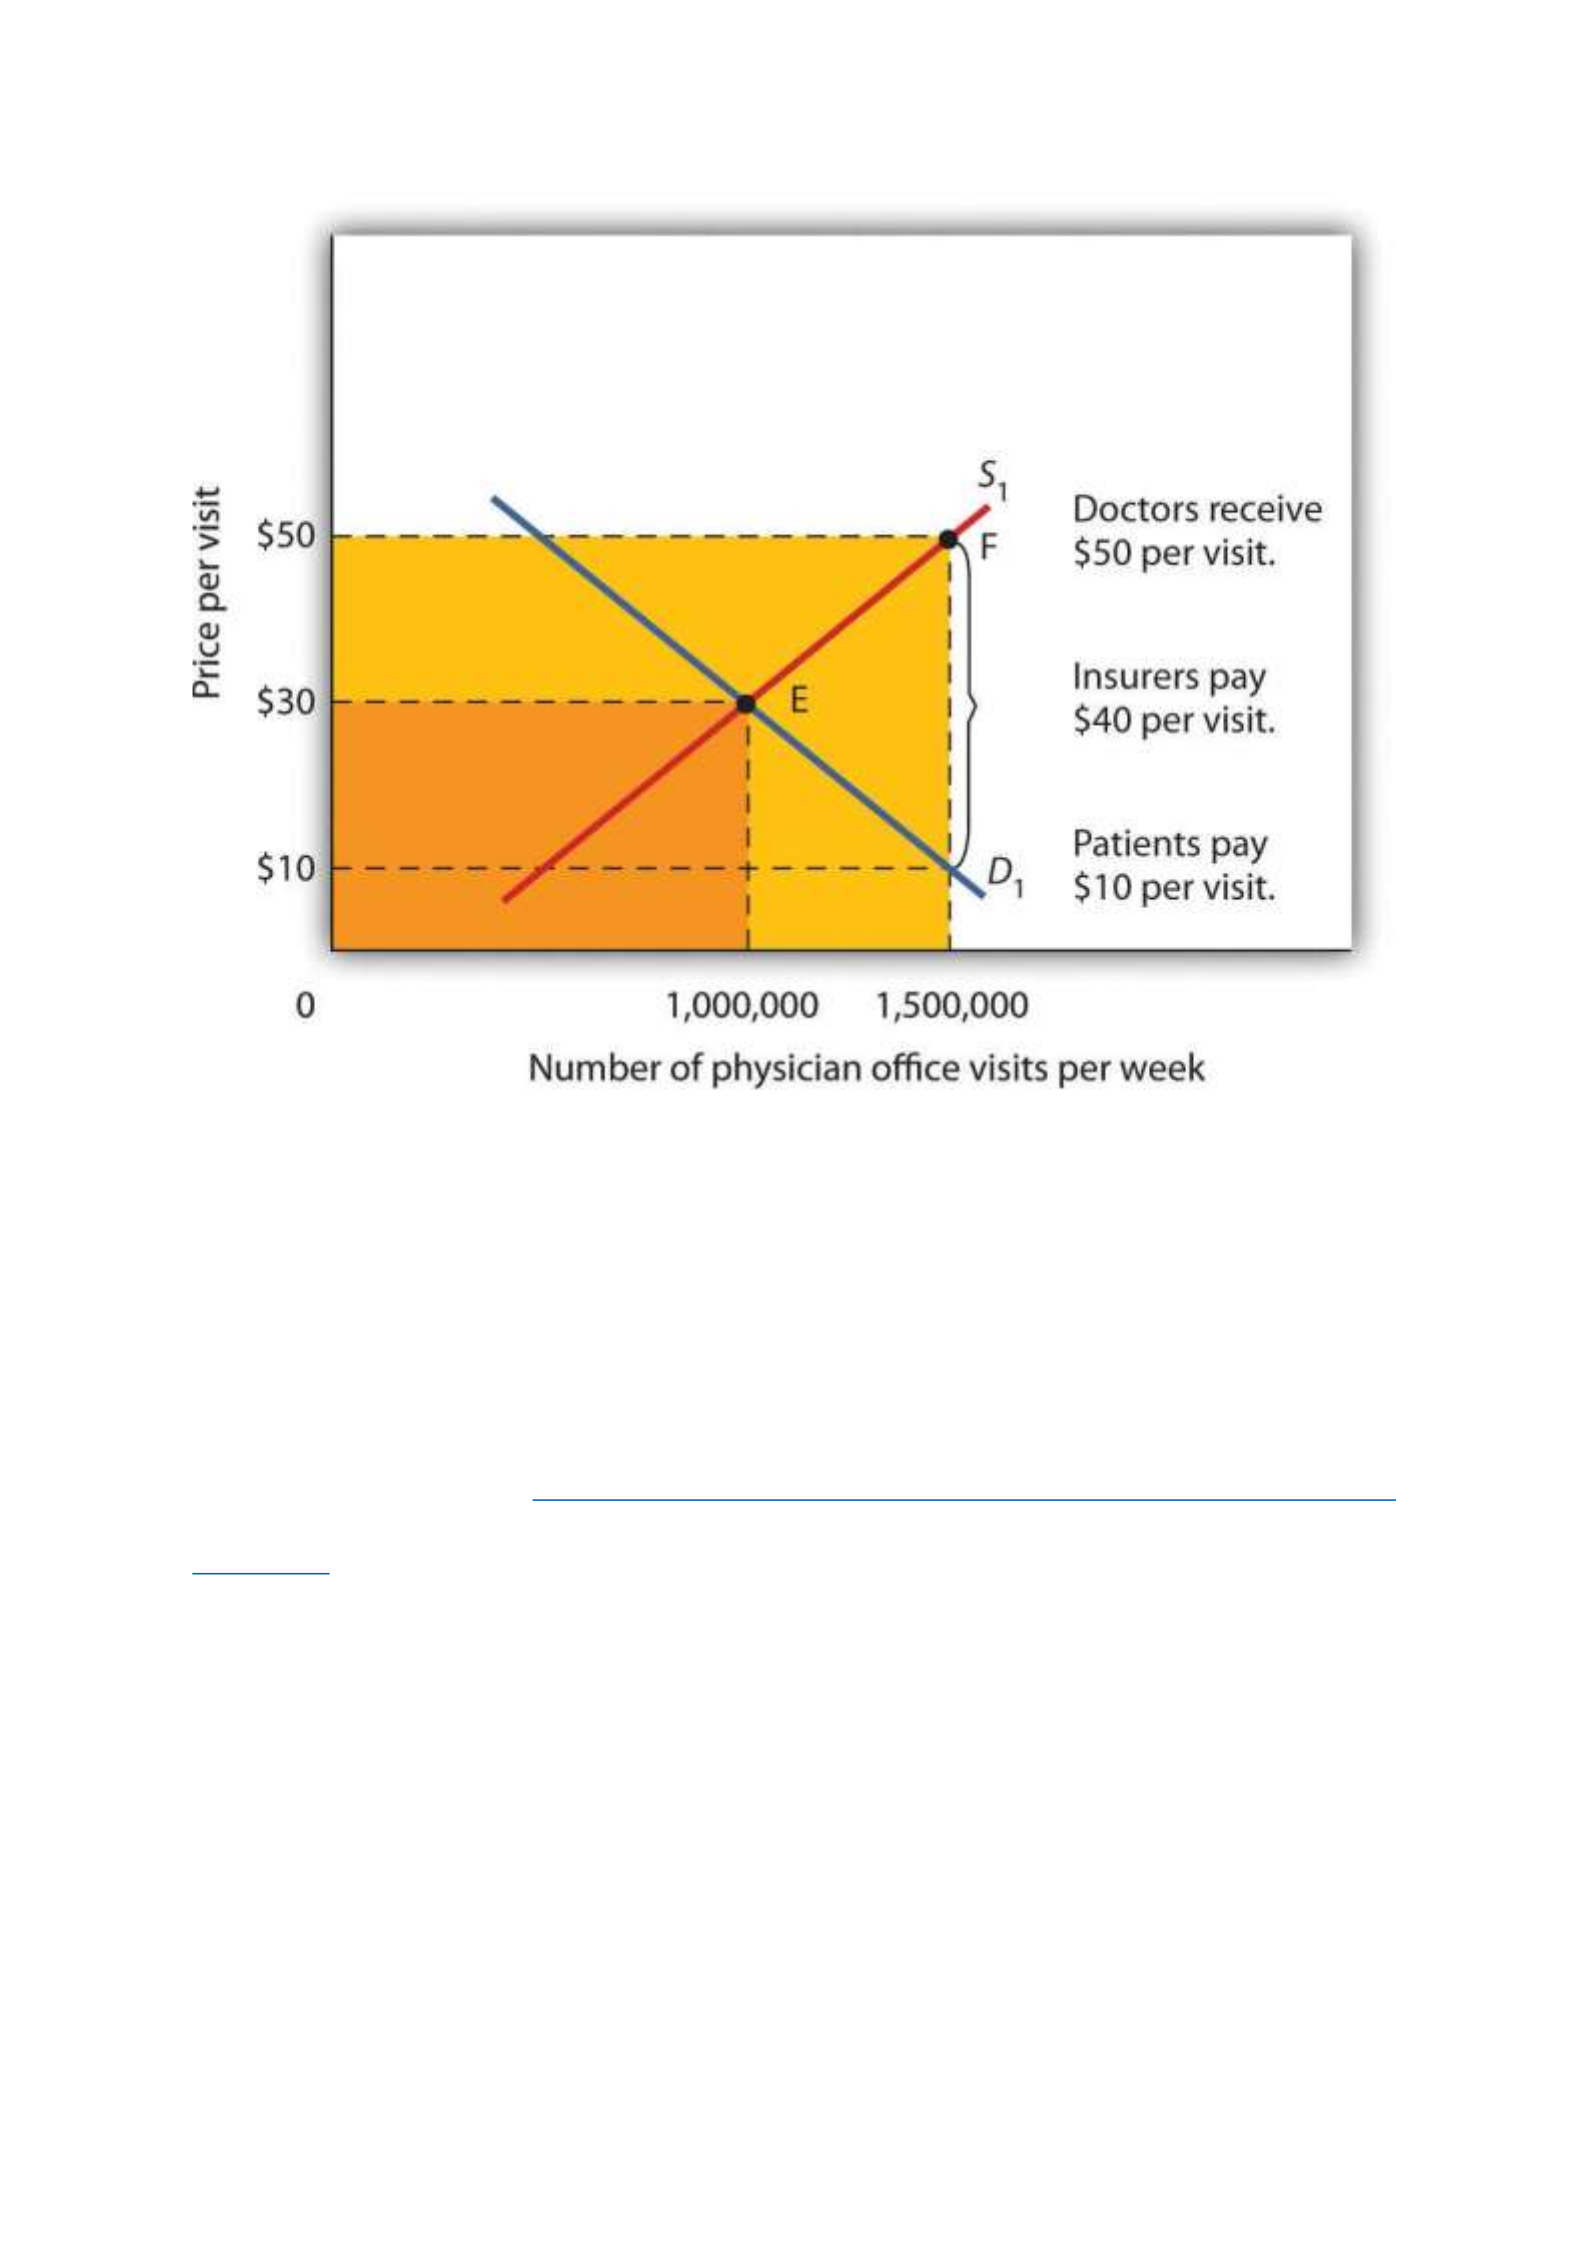
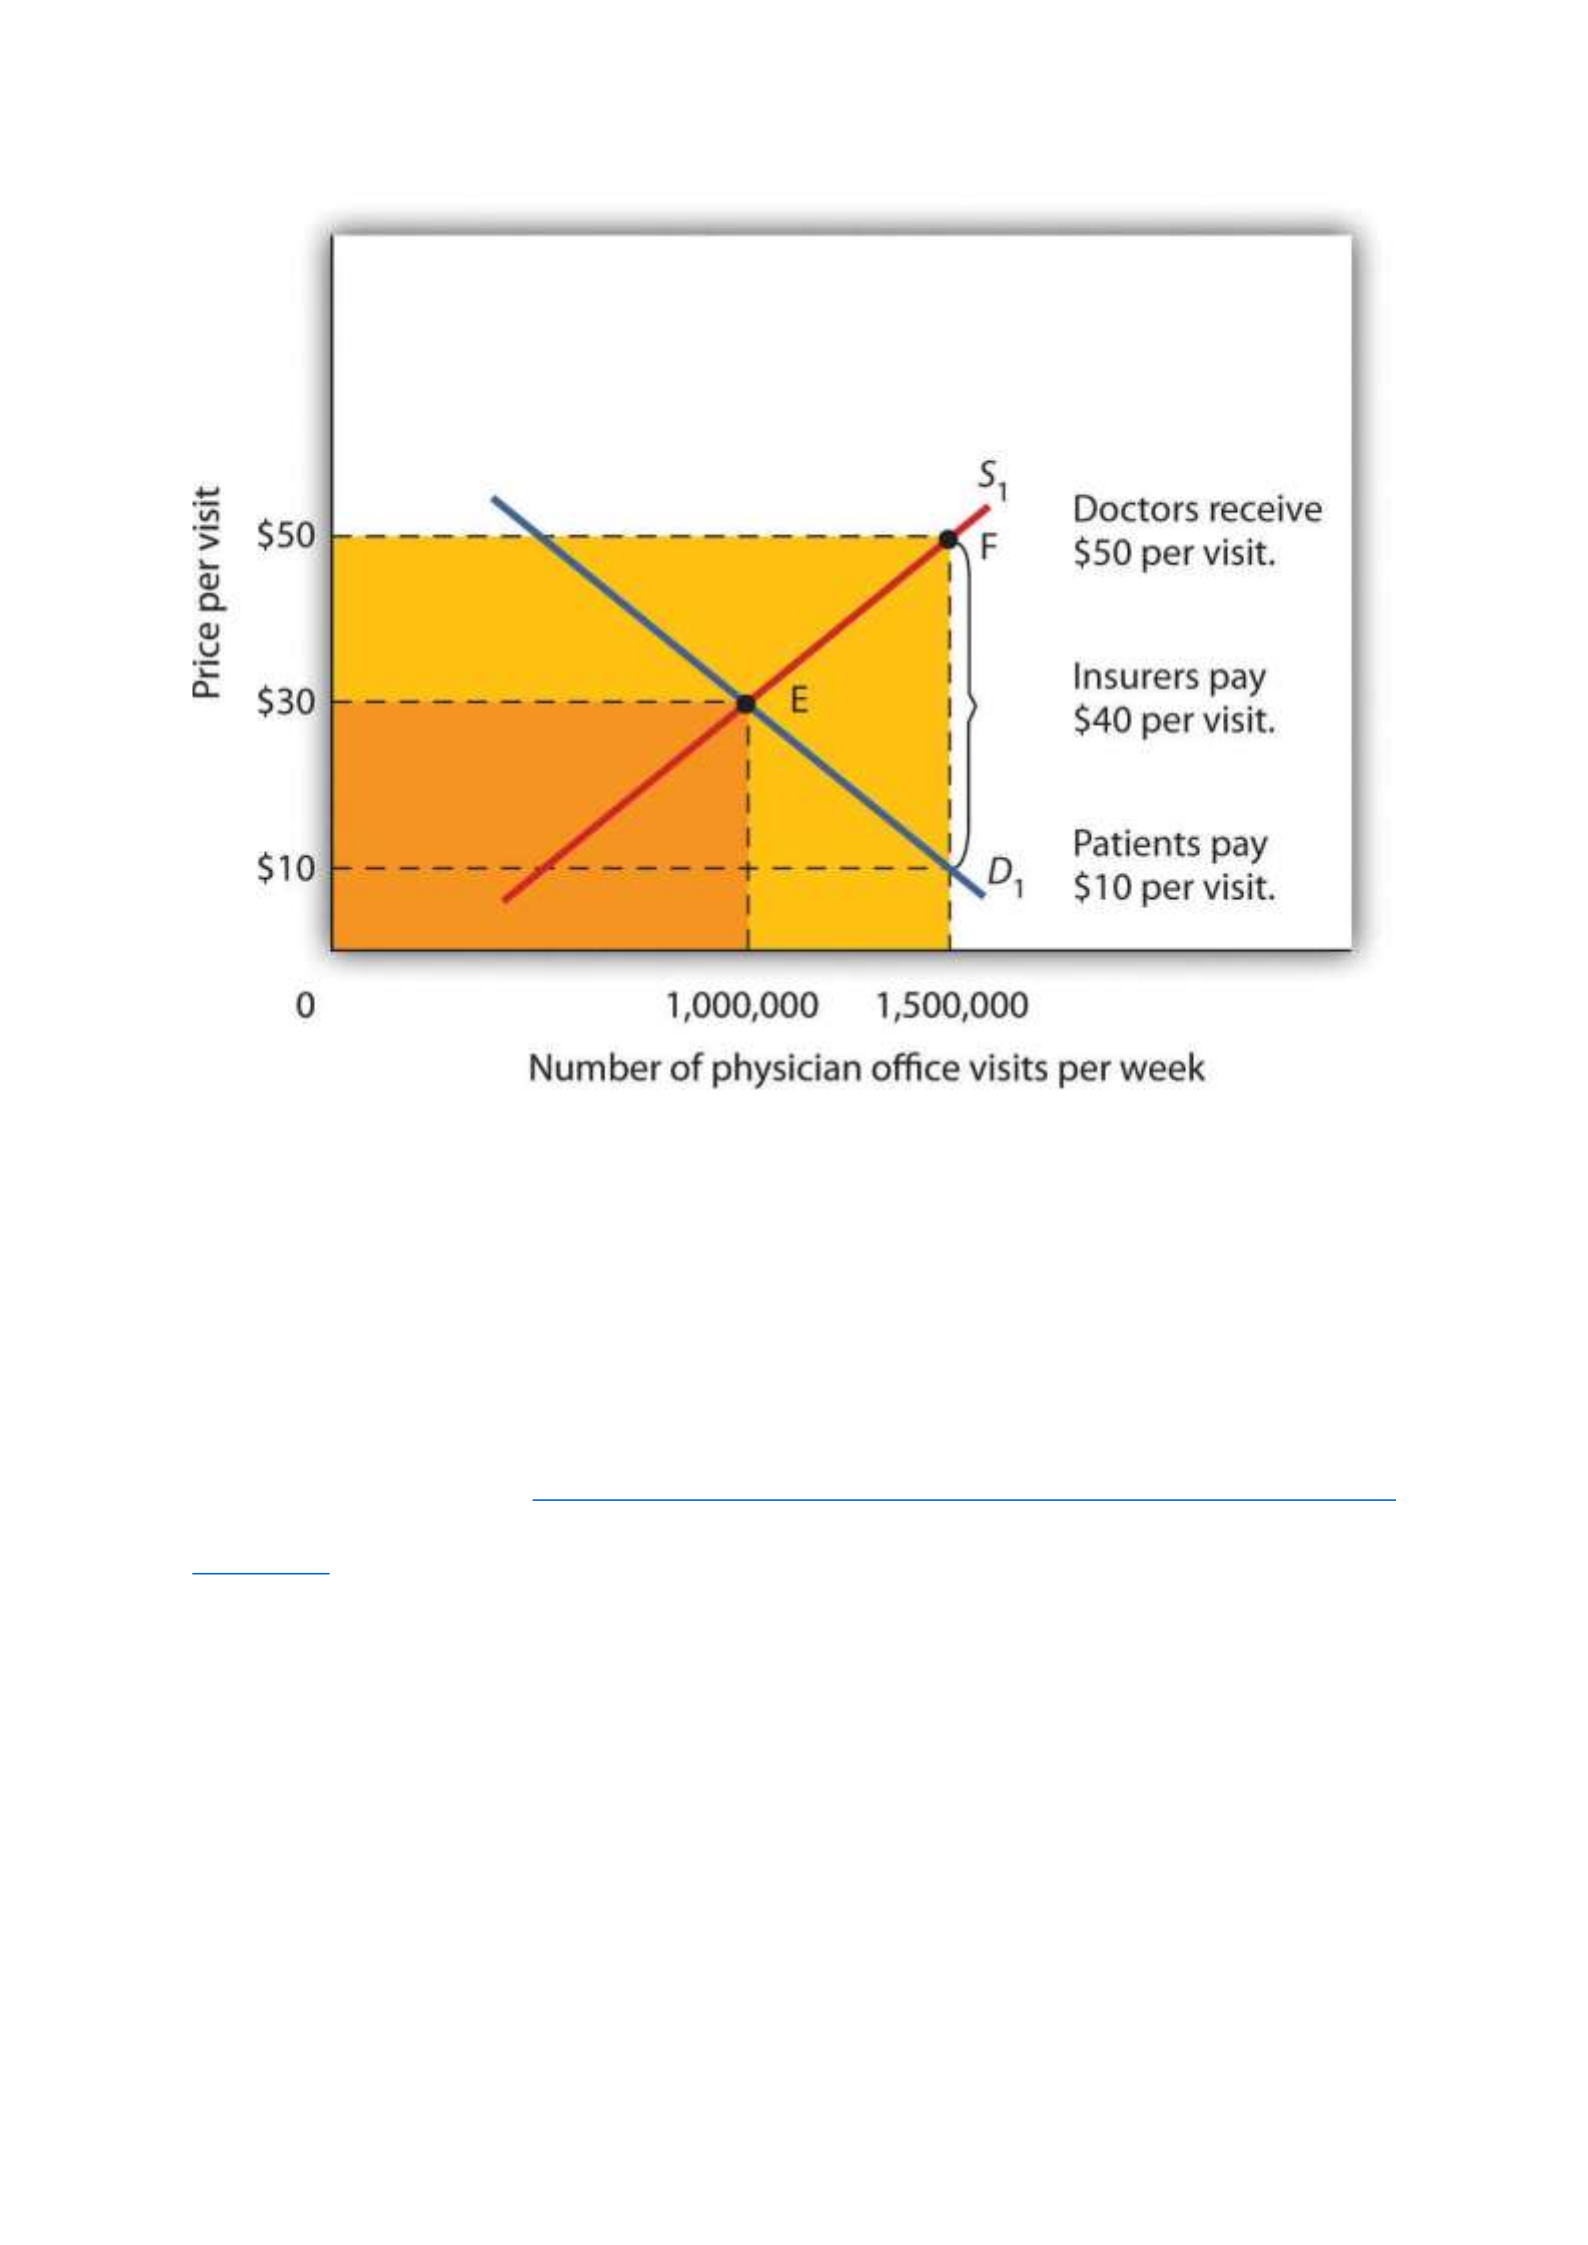
In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
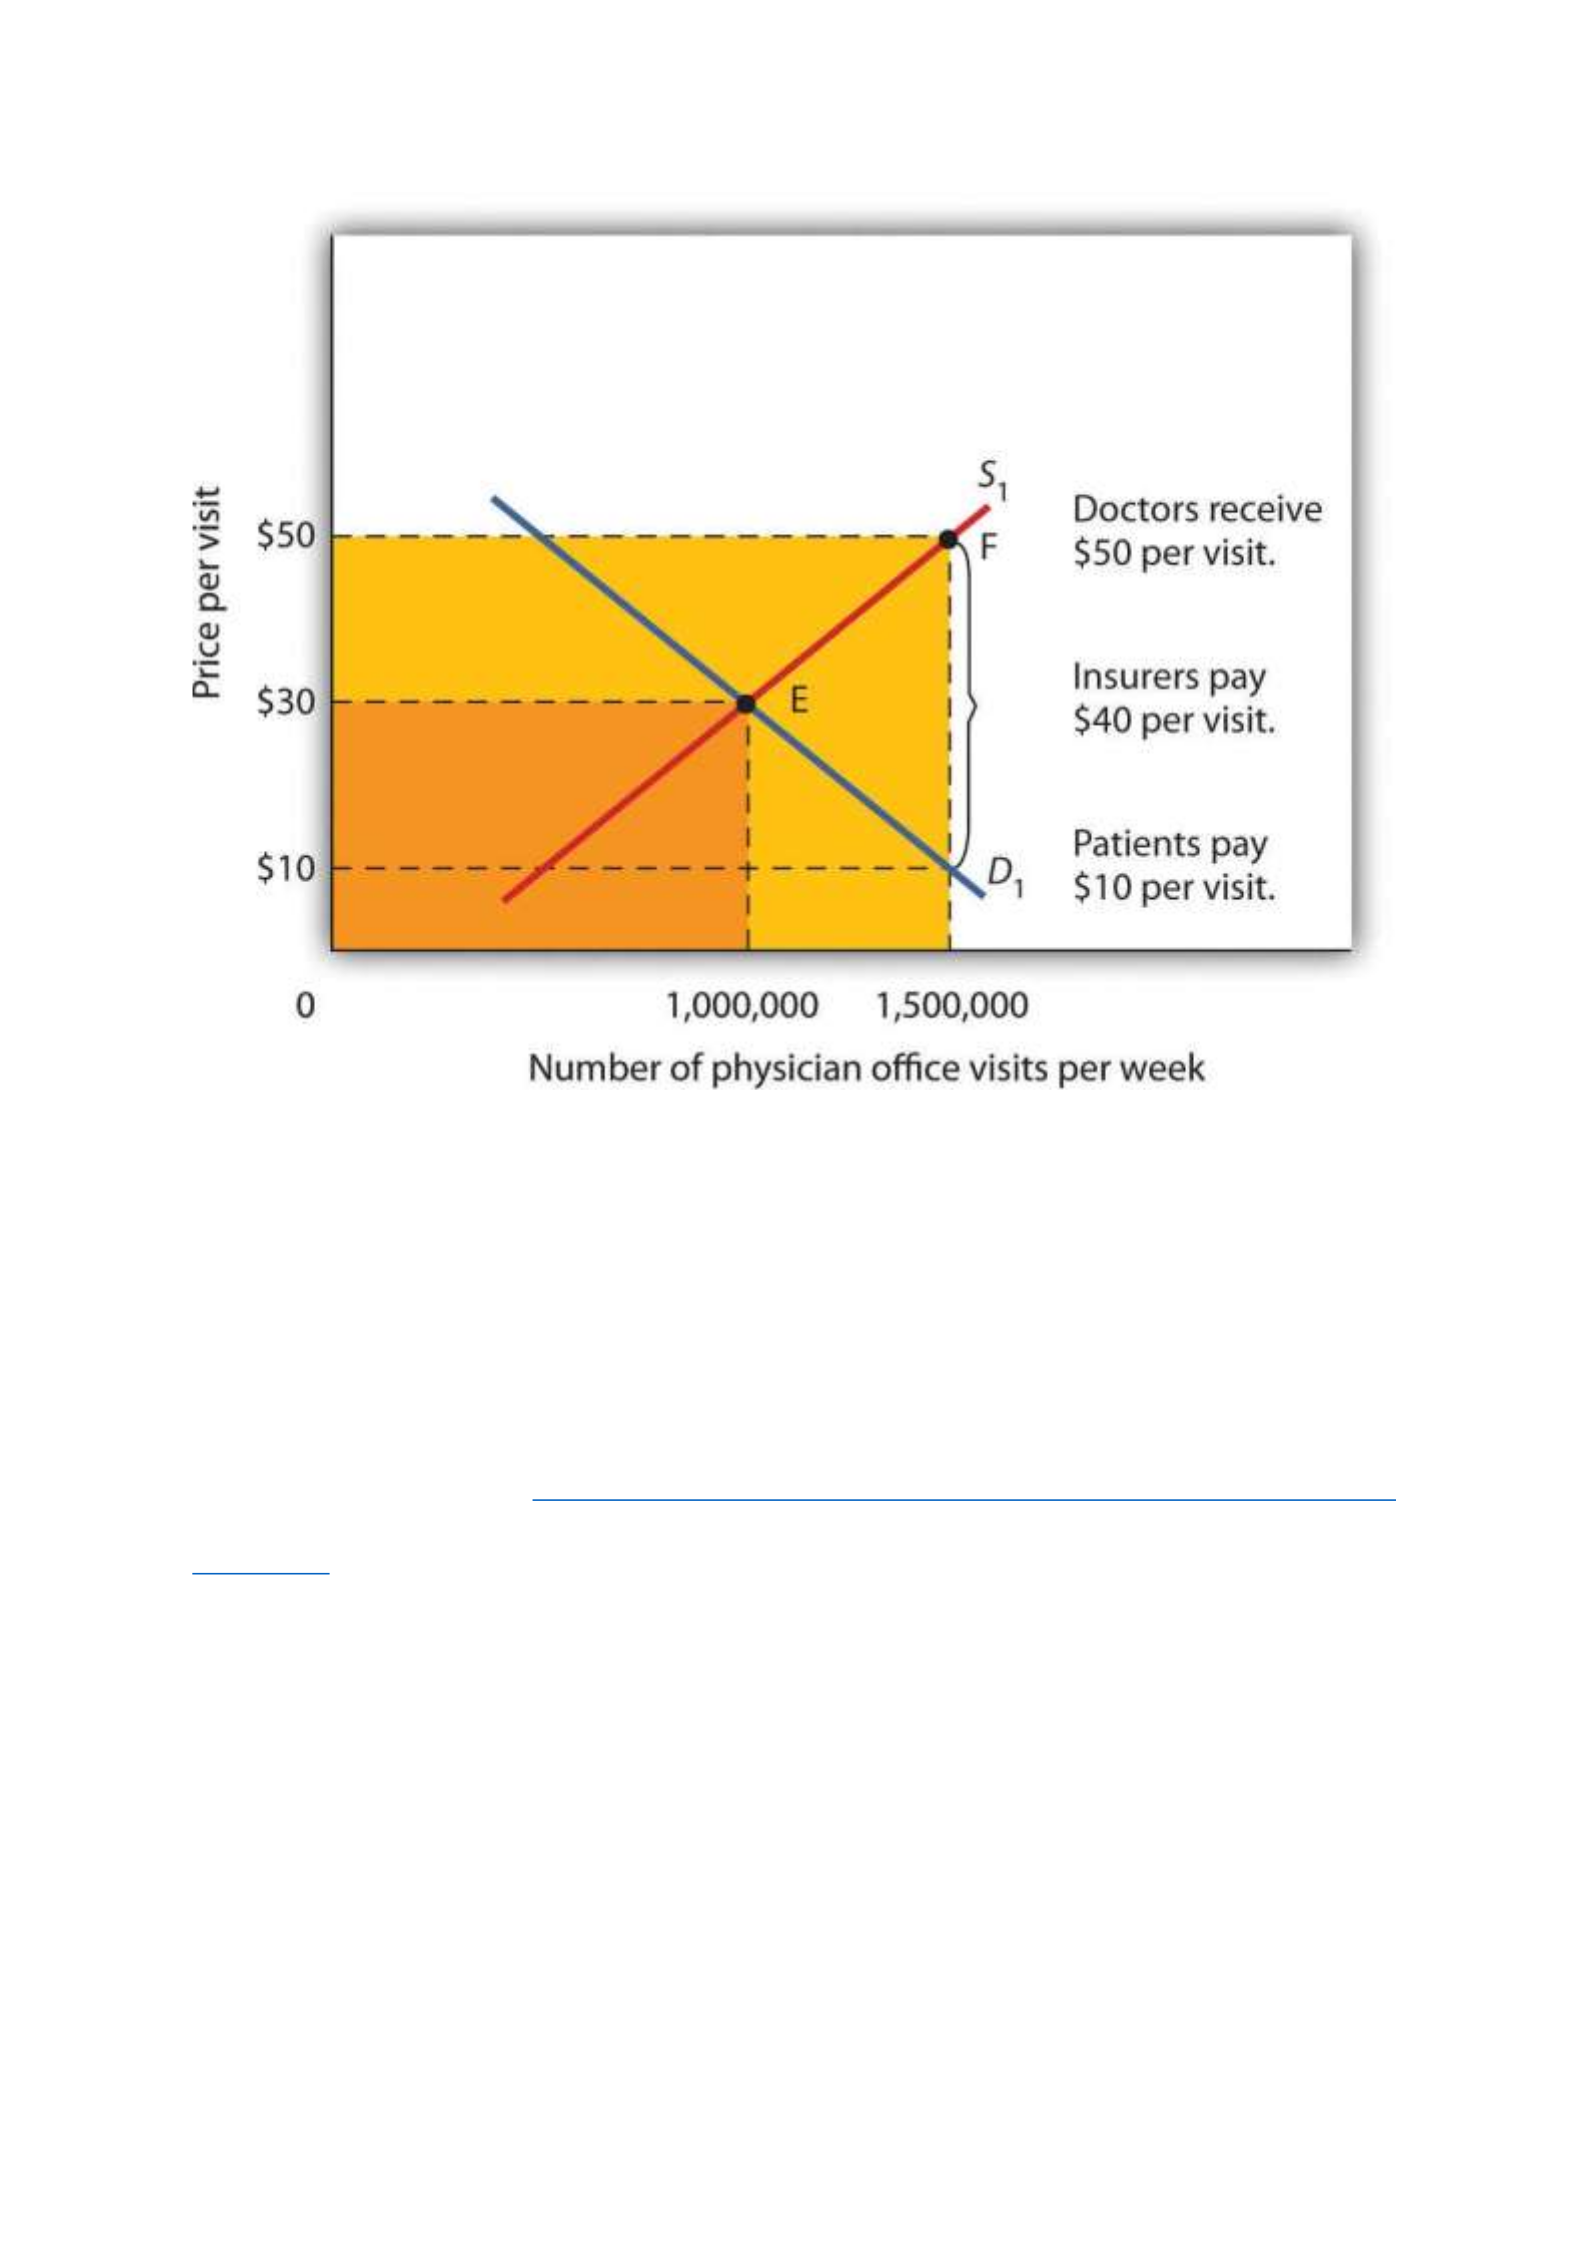
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
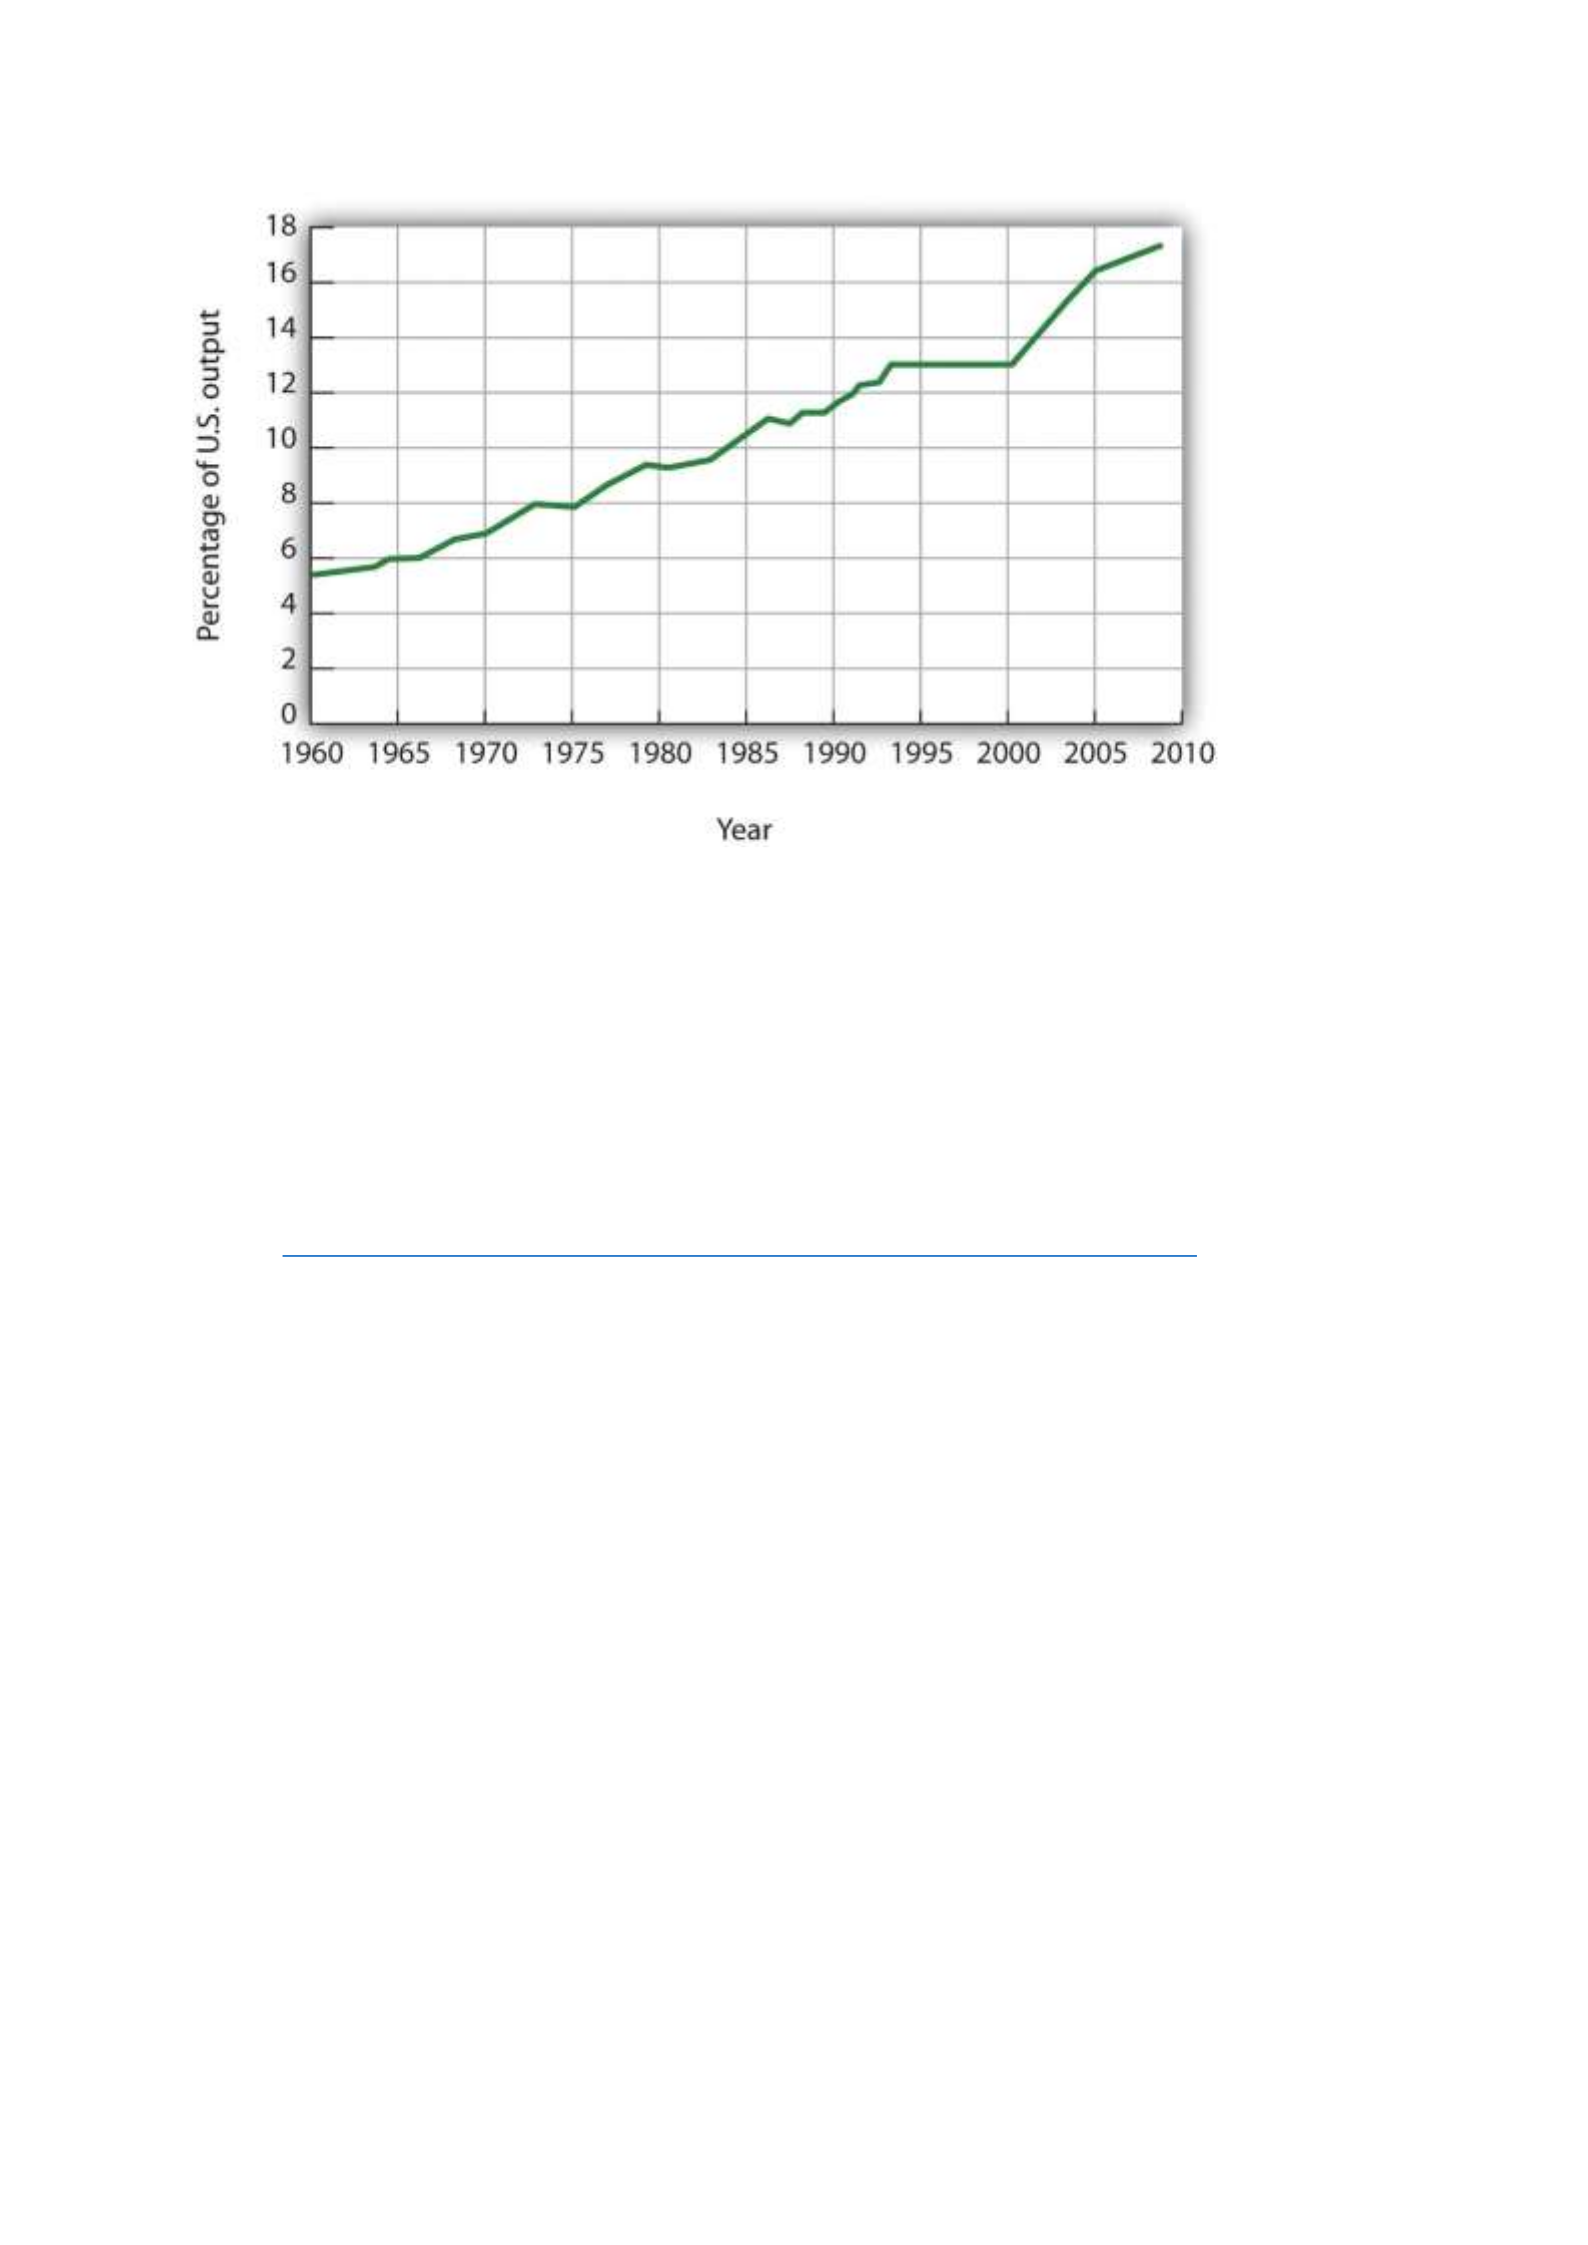
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
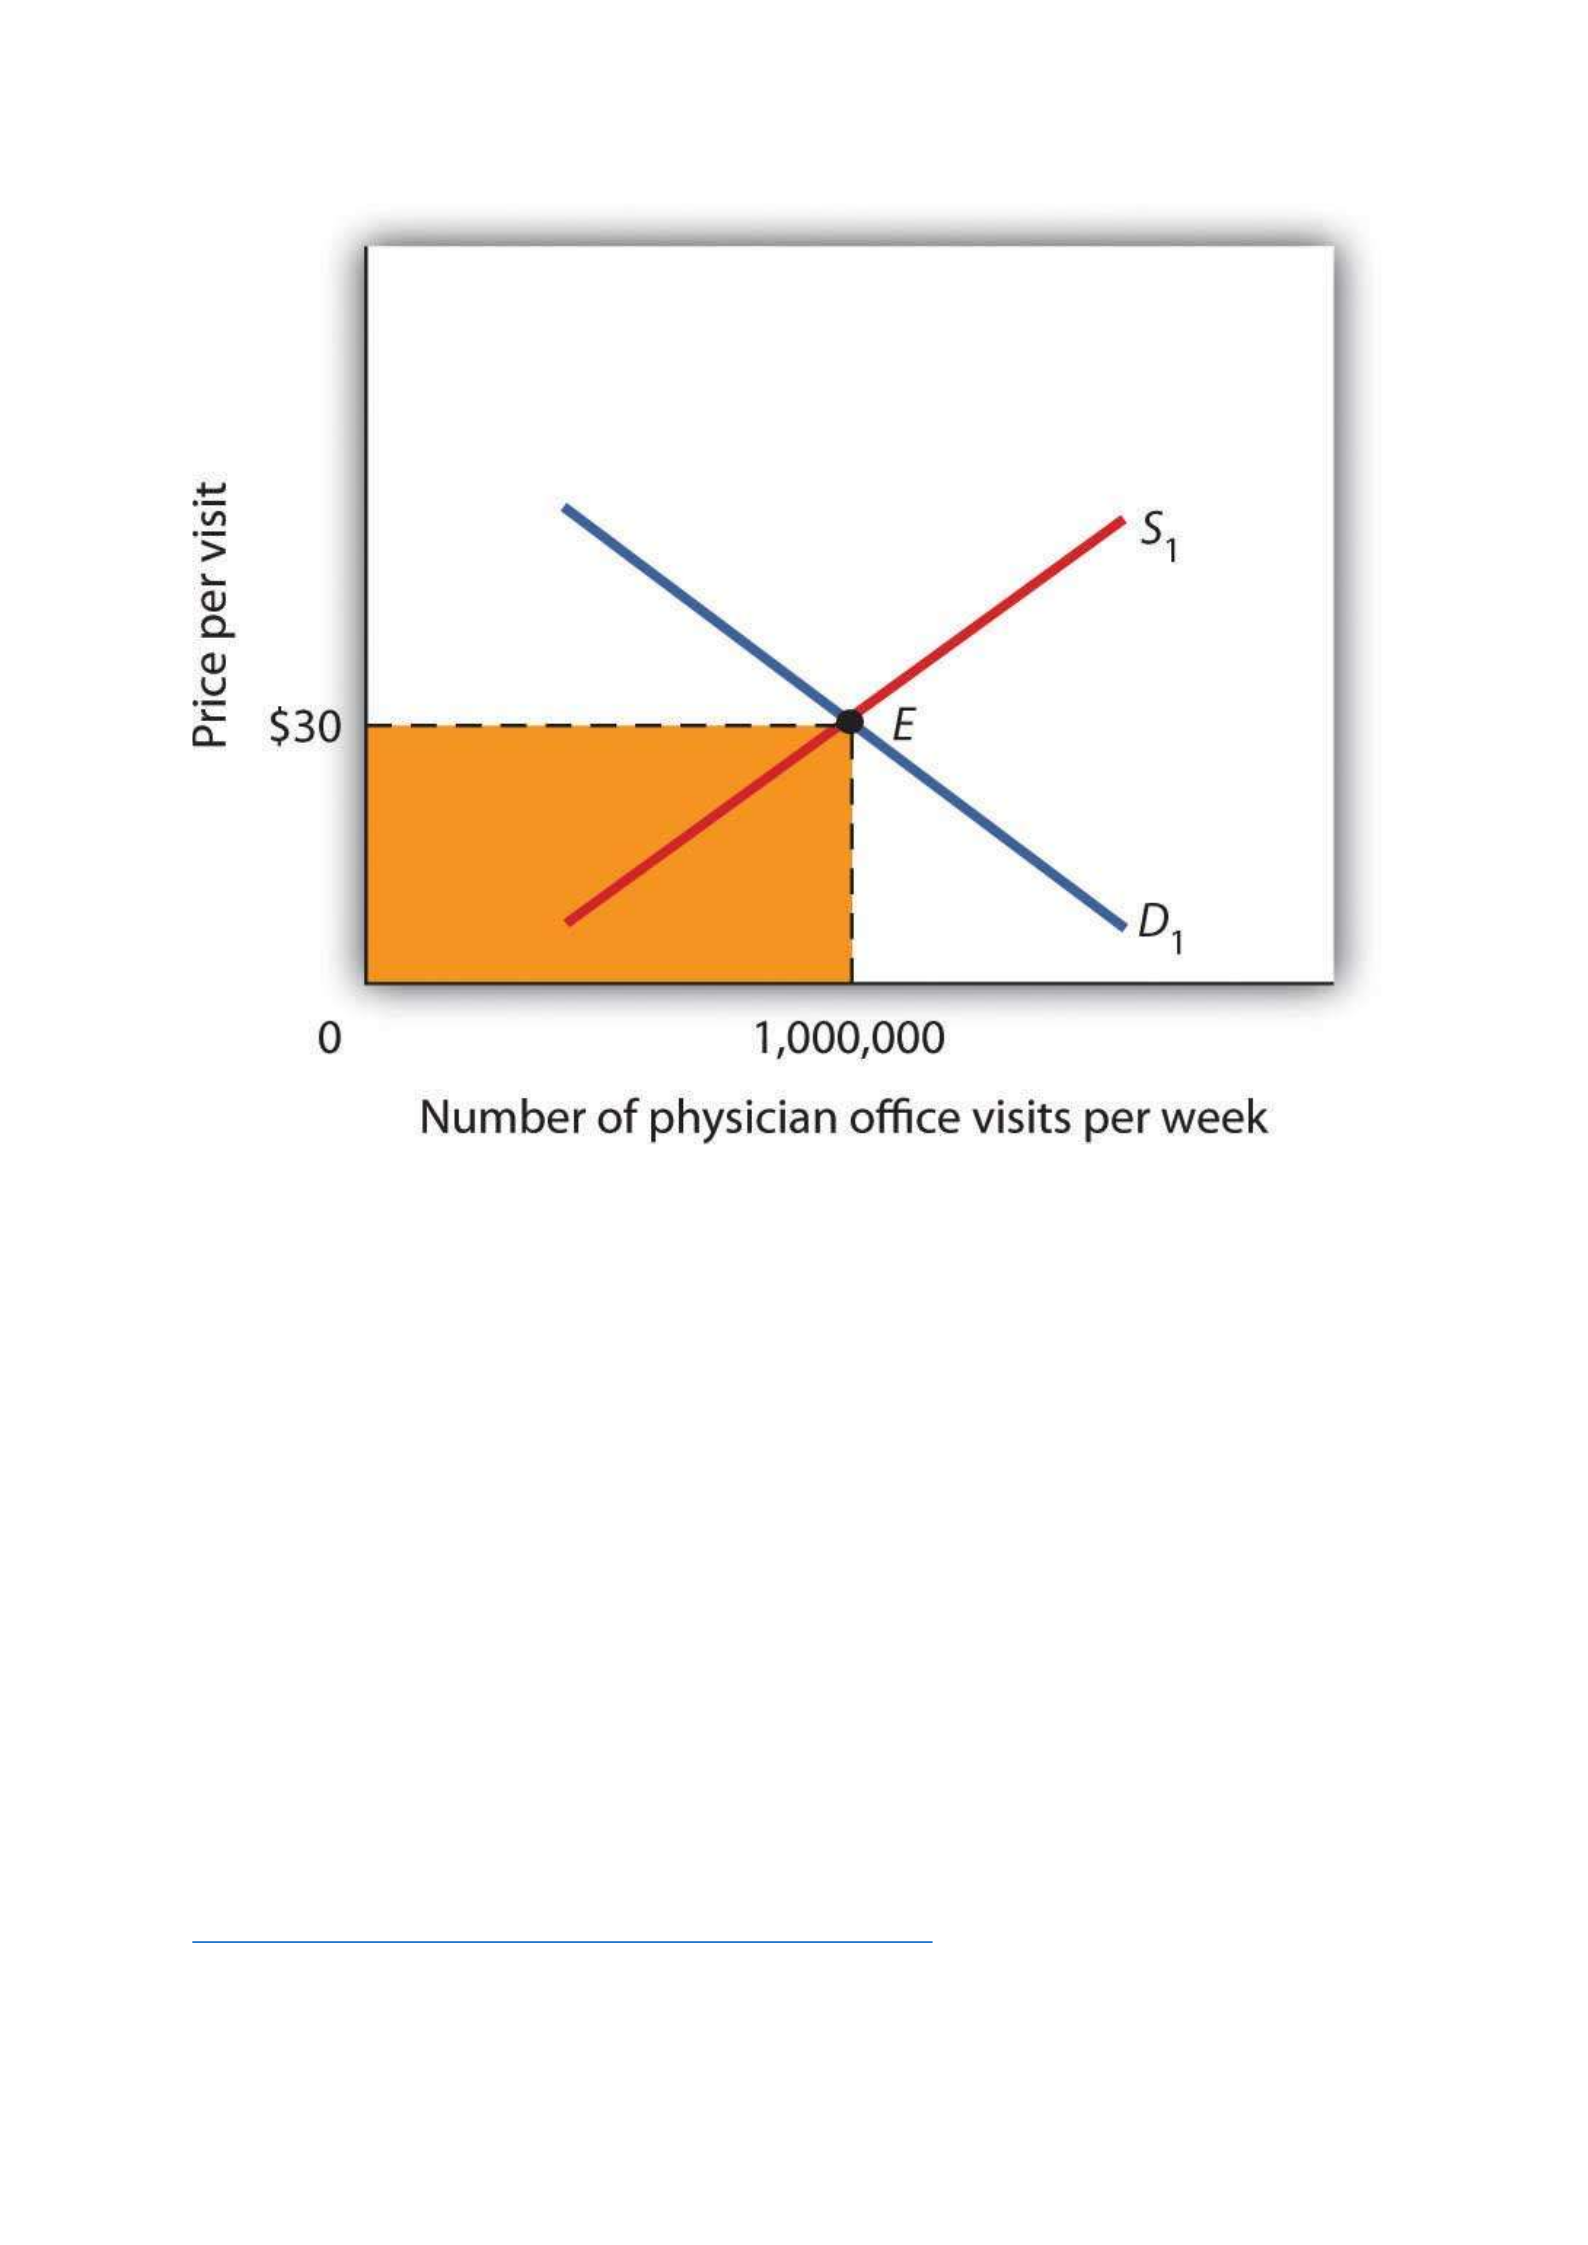
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
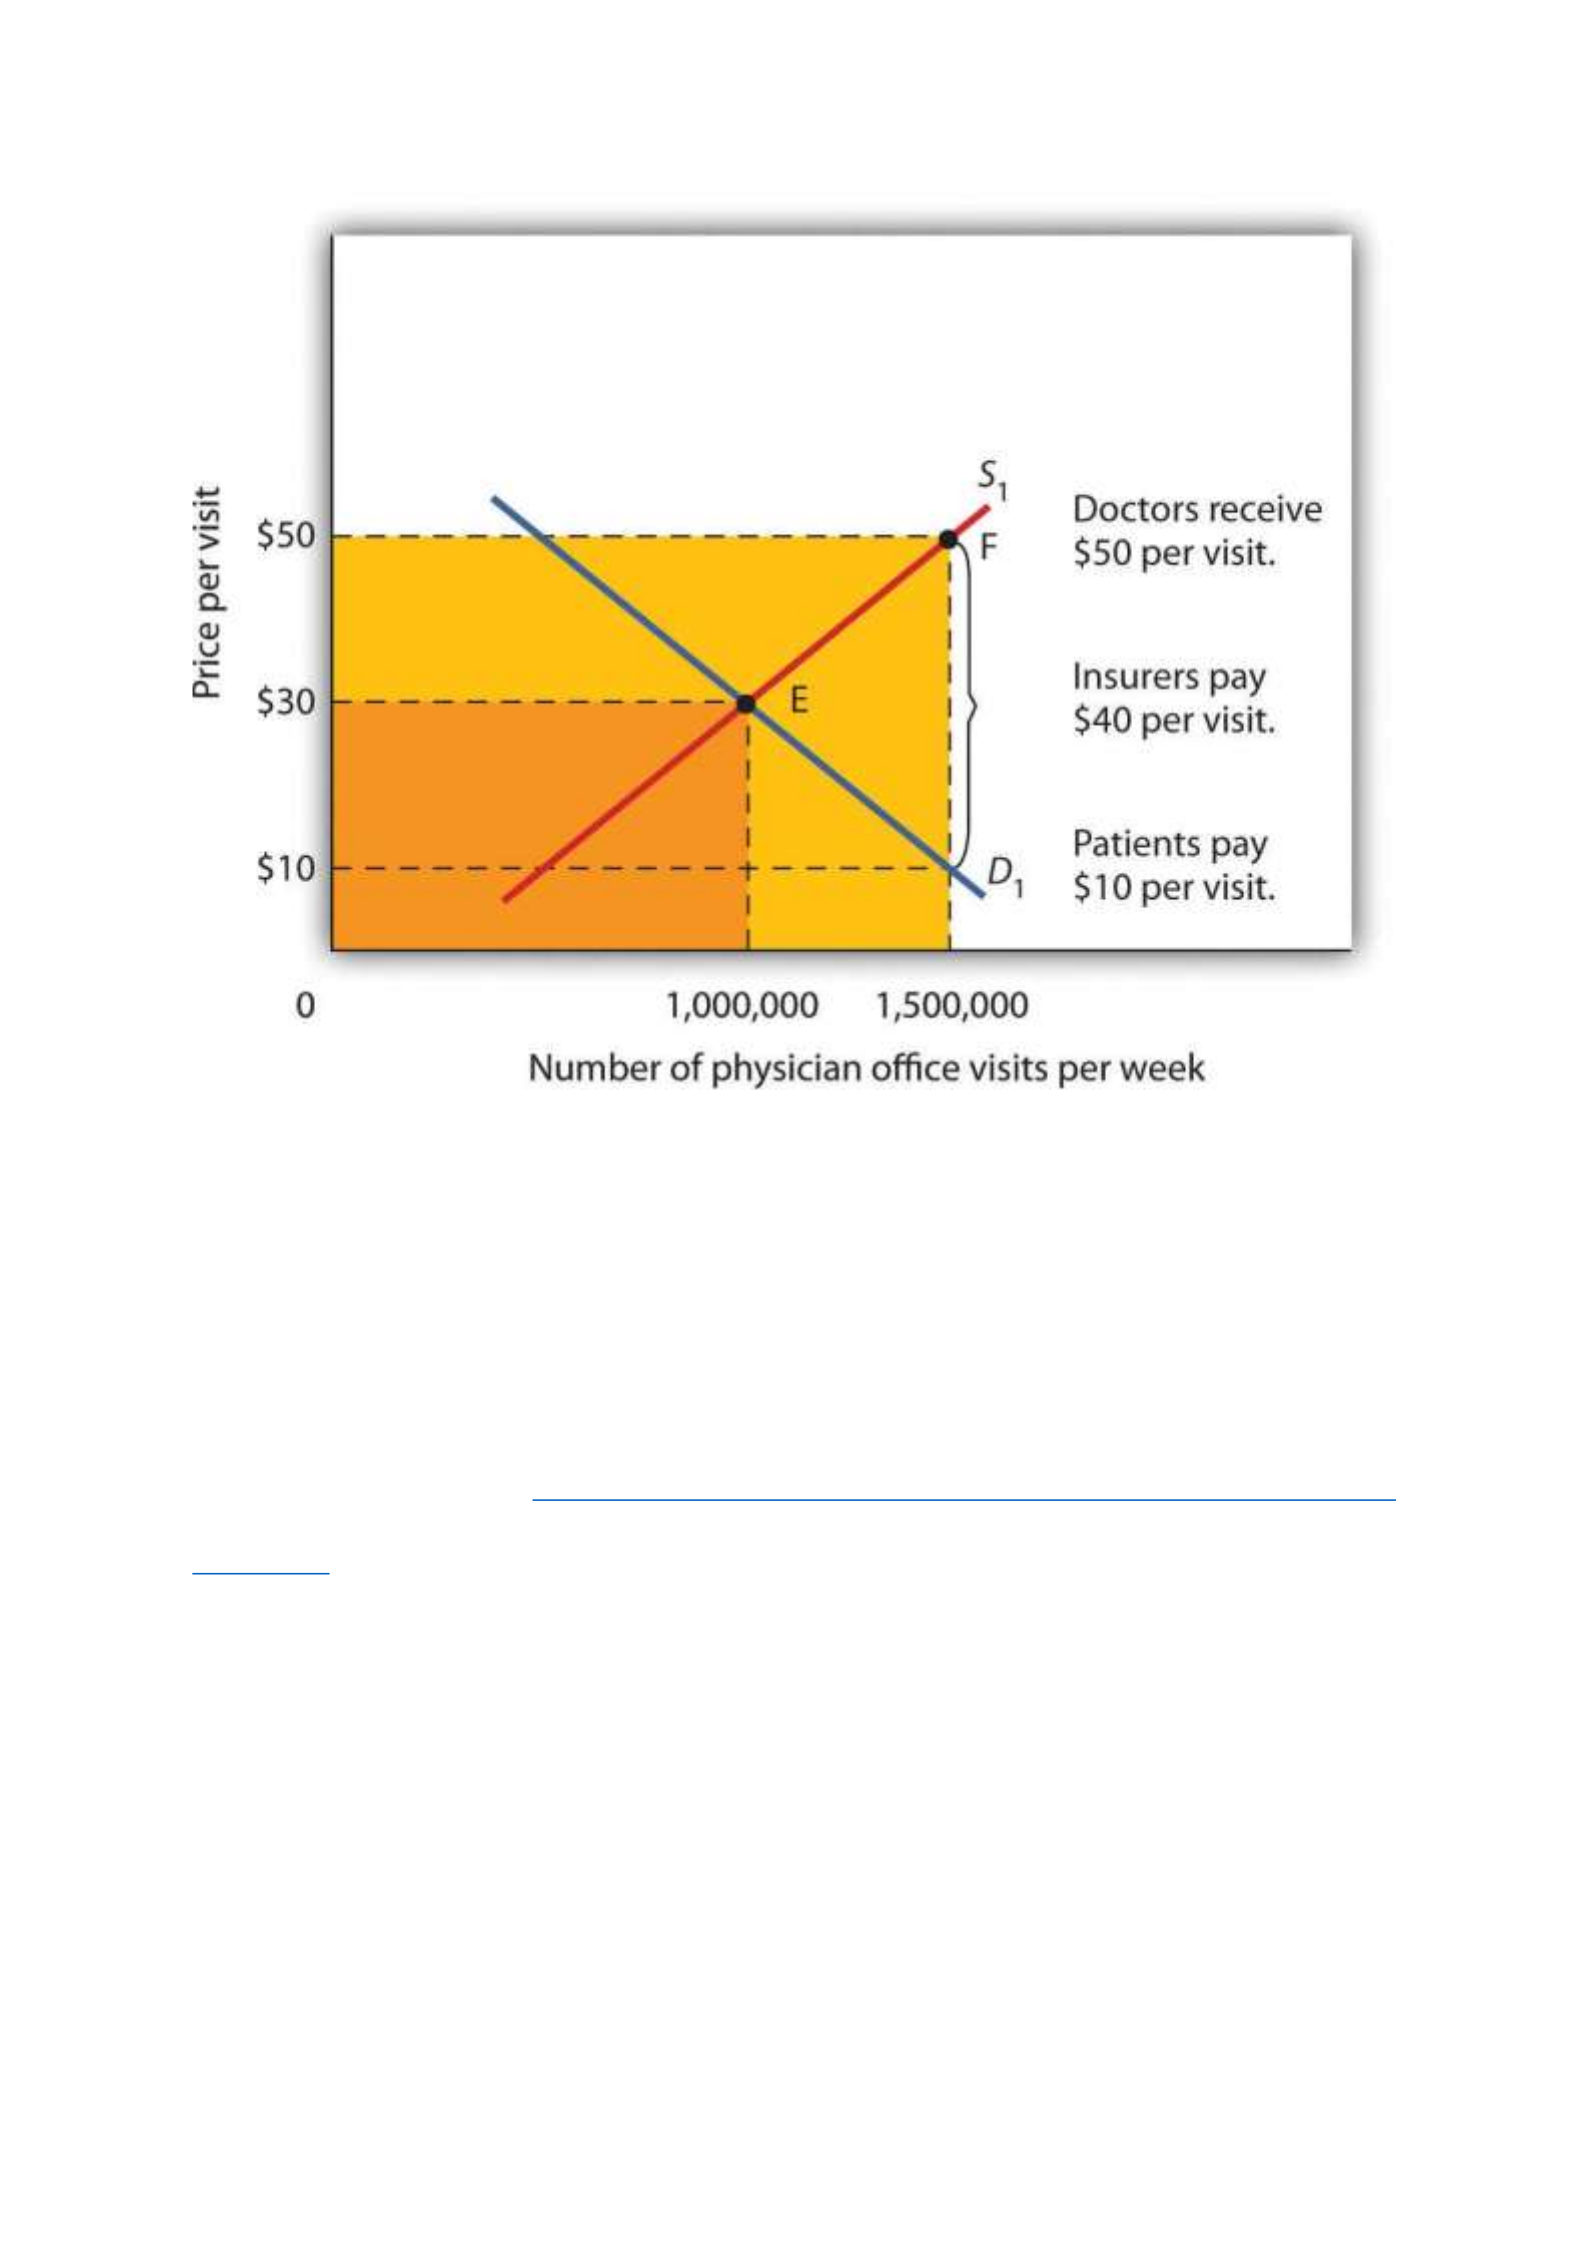
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
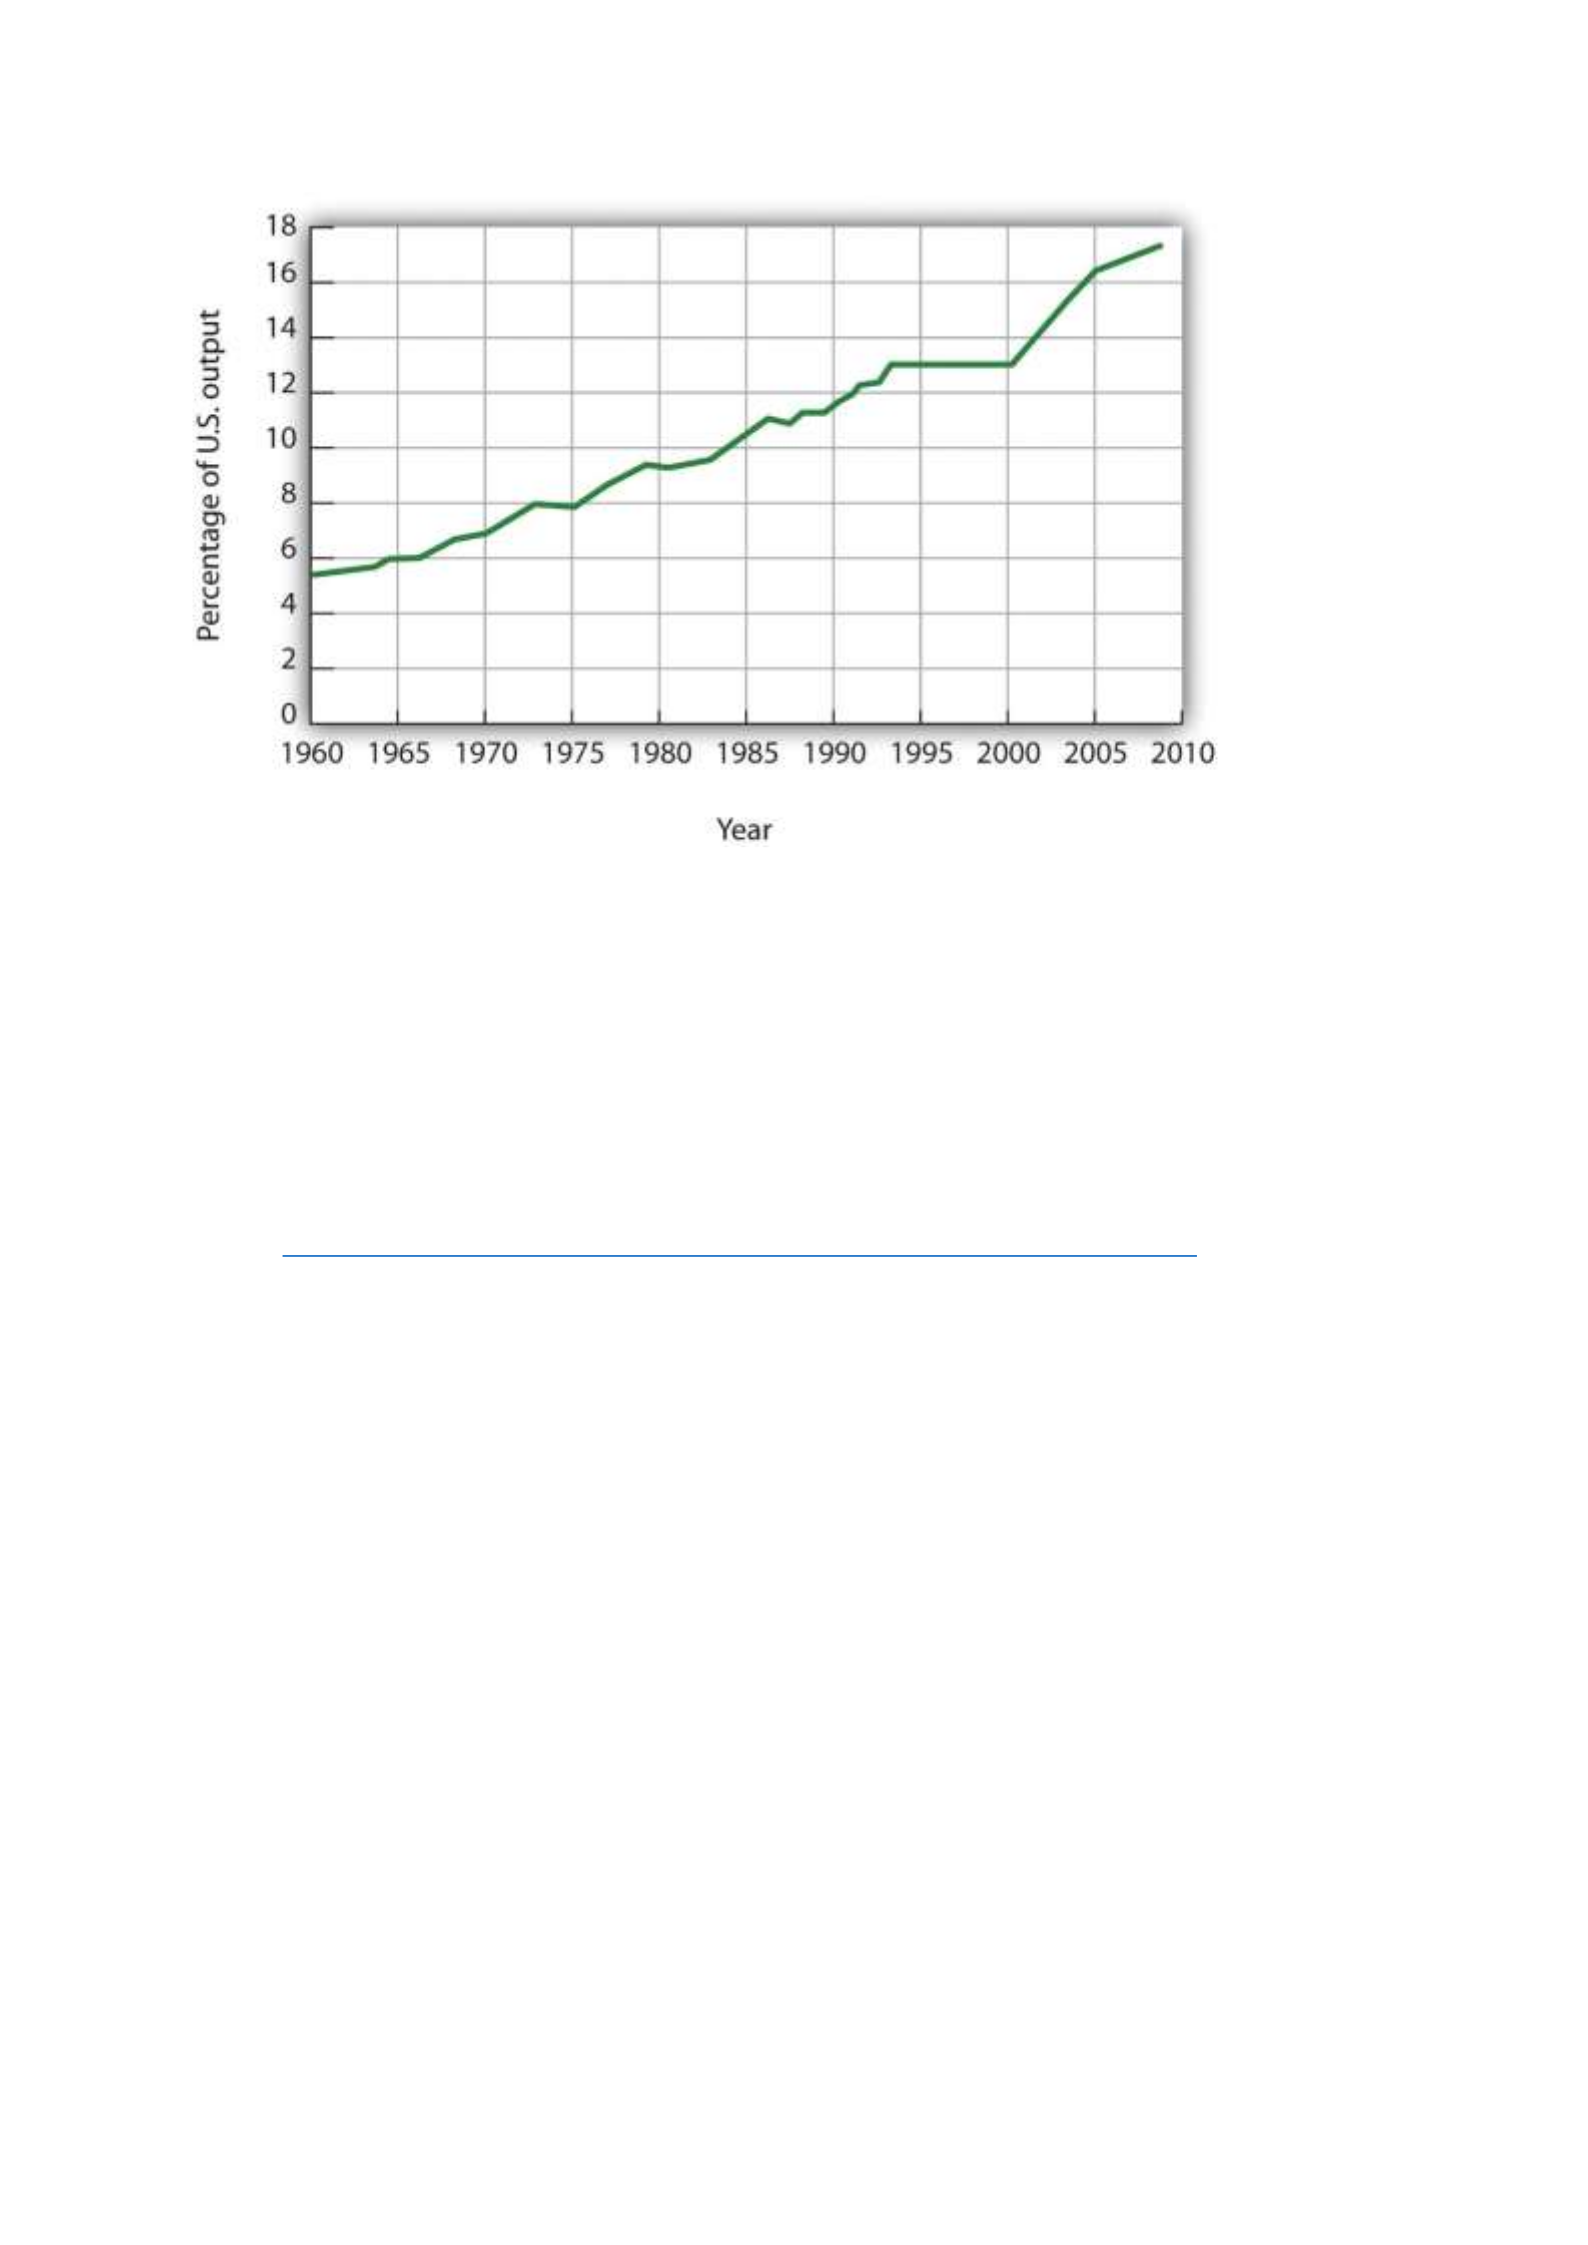
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
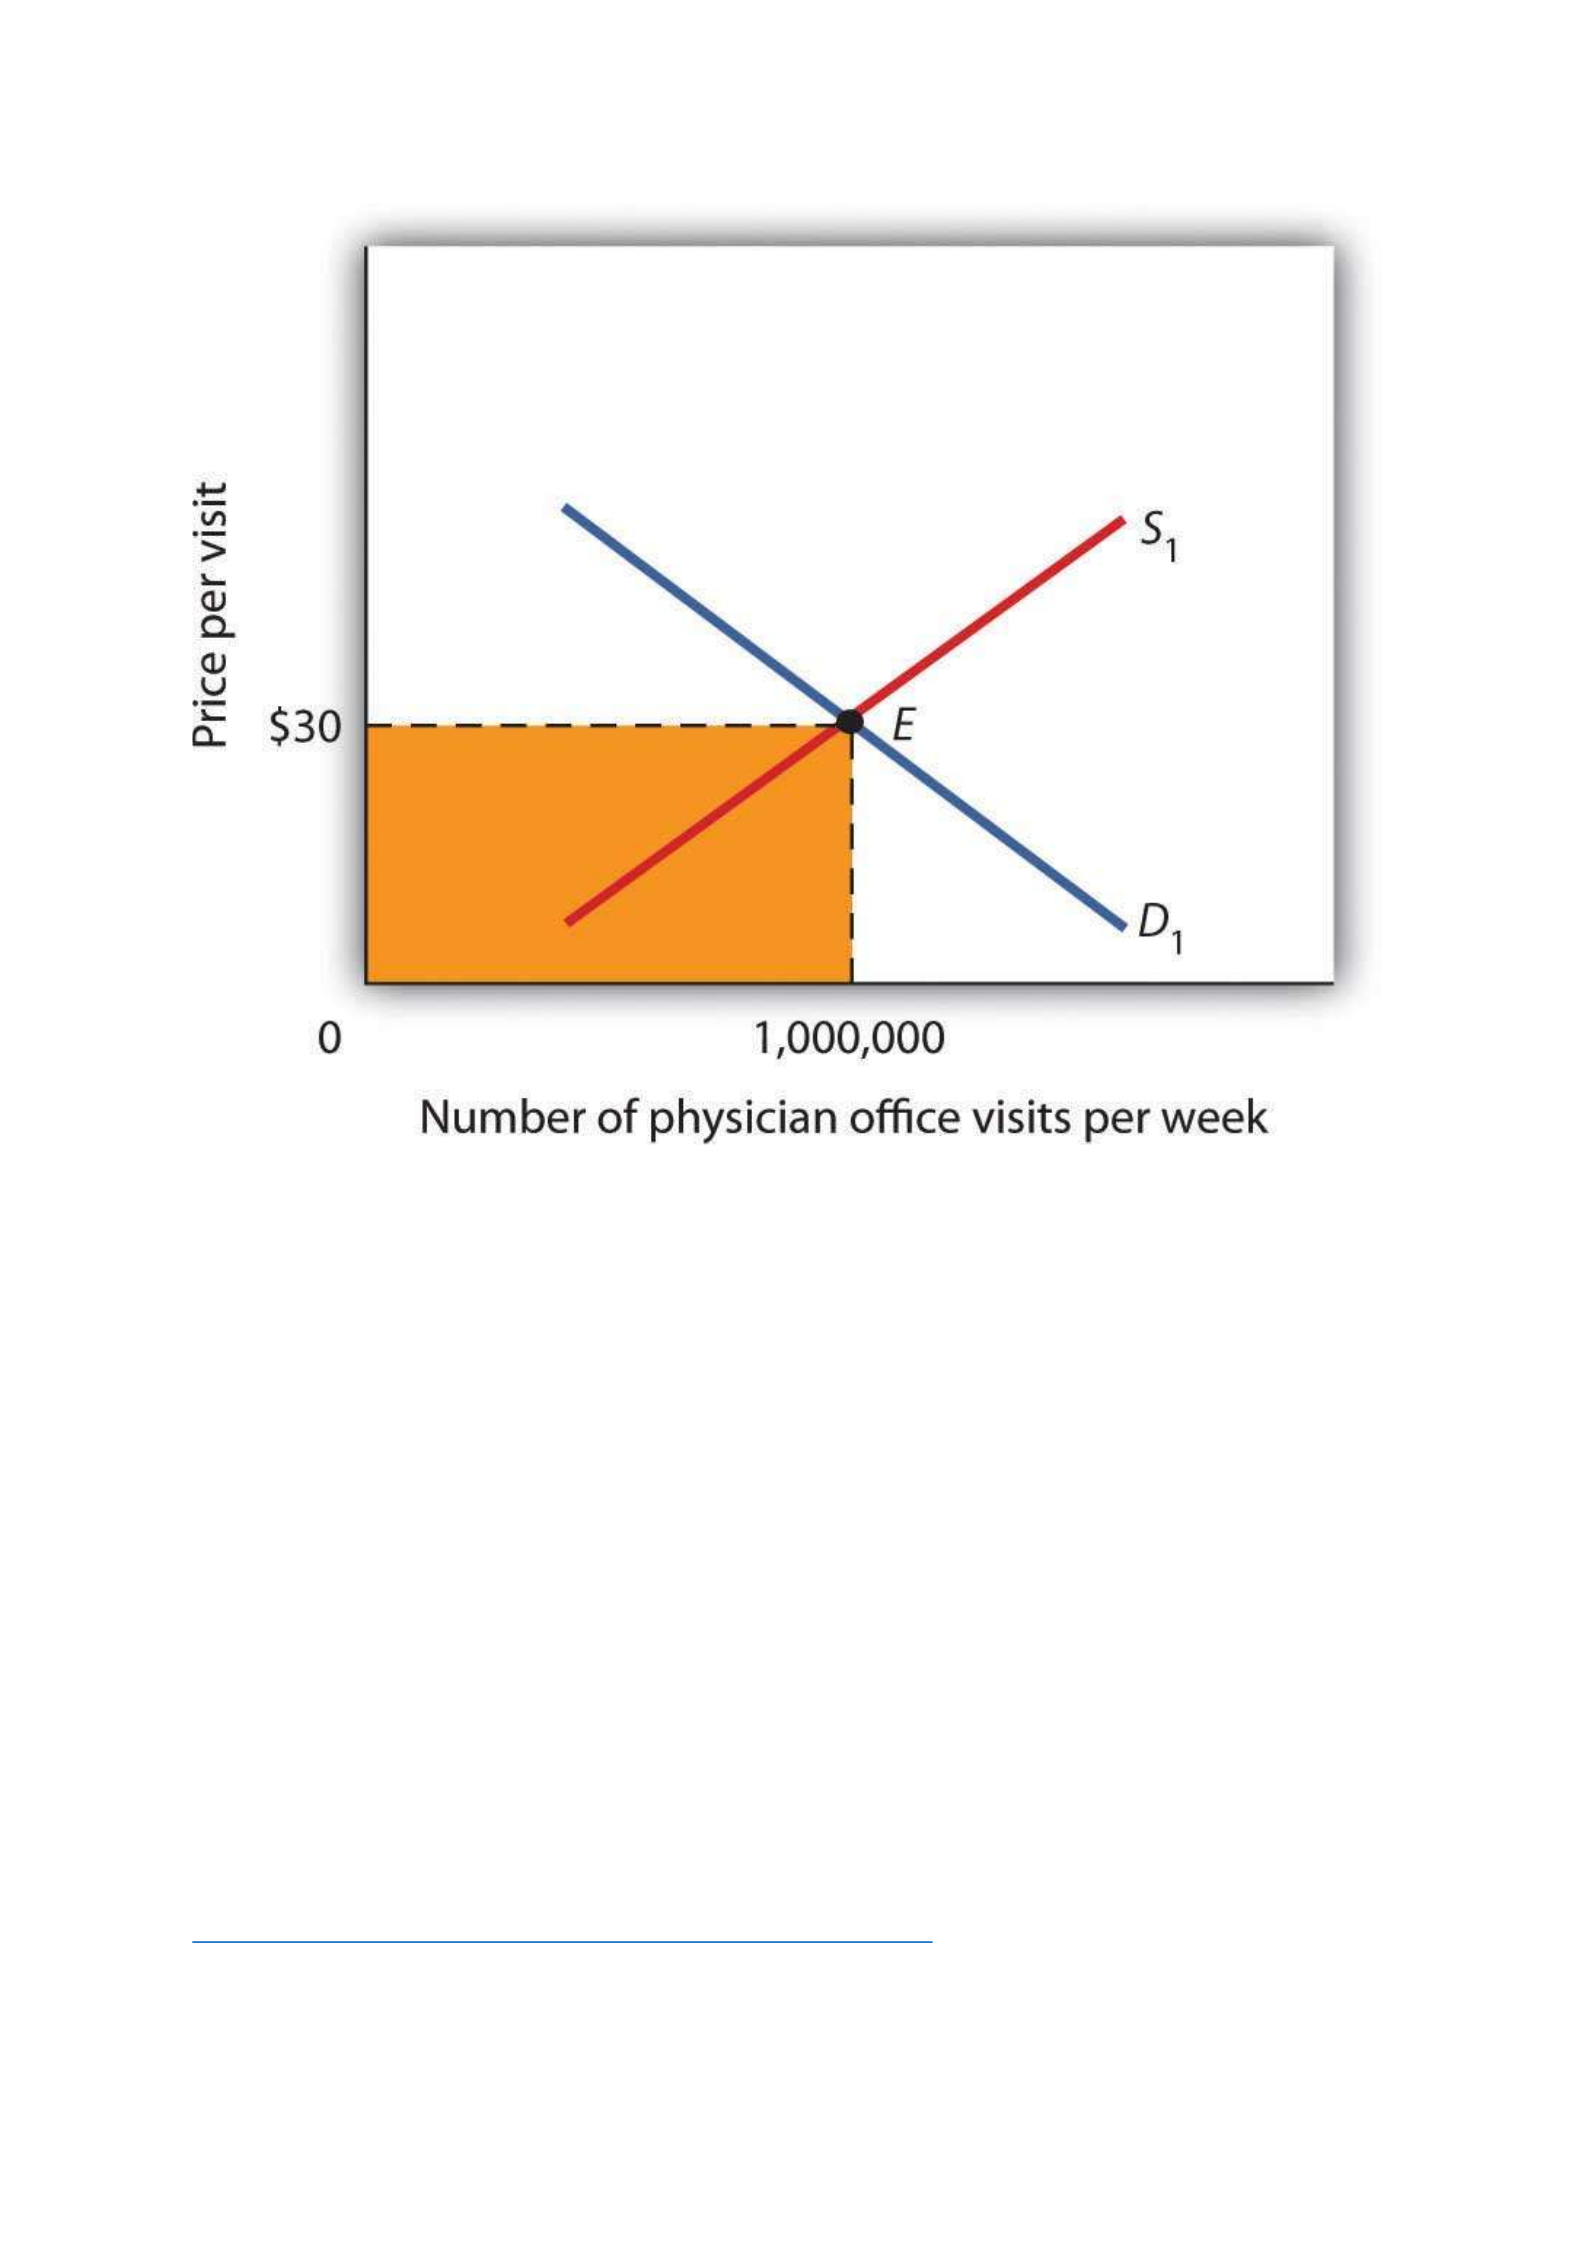
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
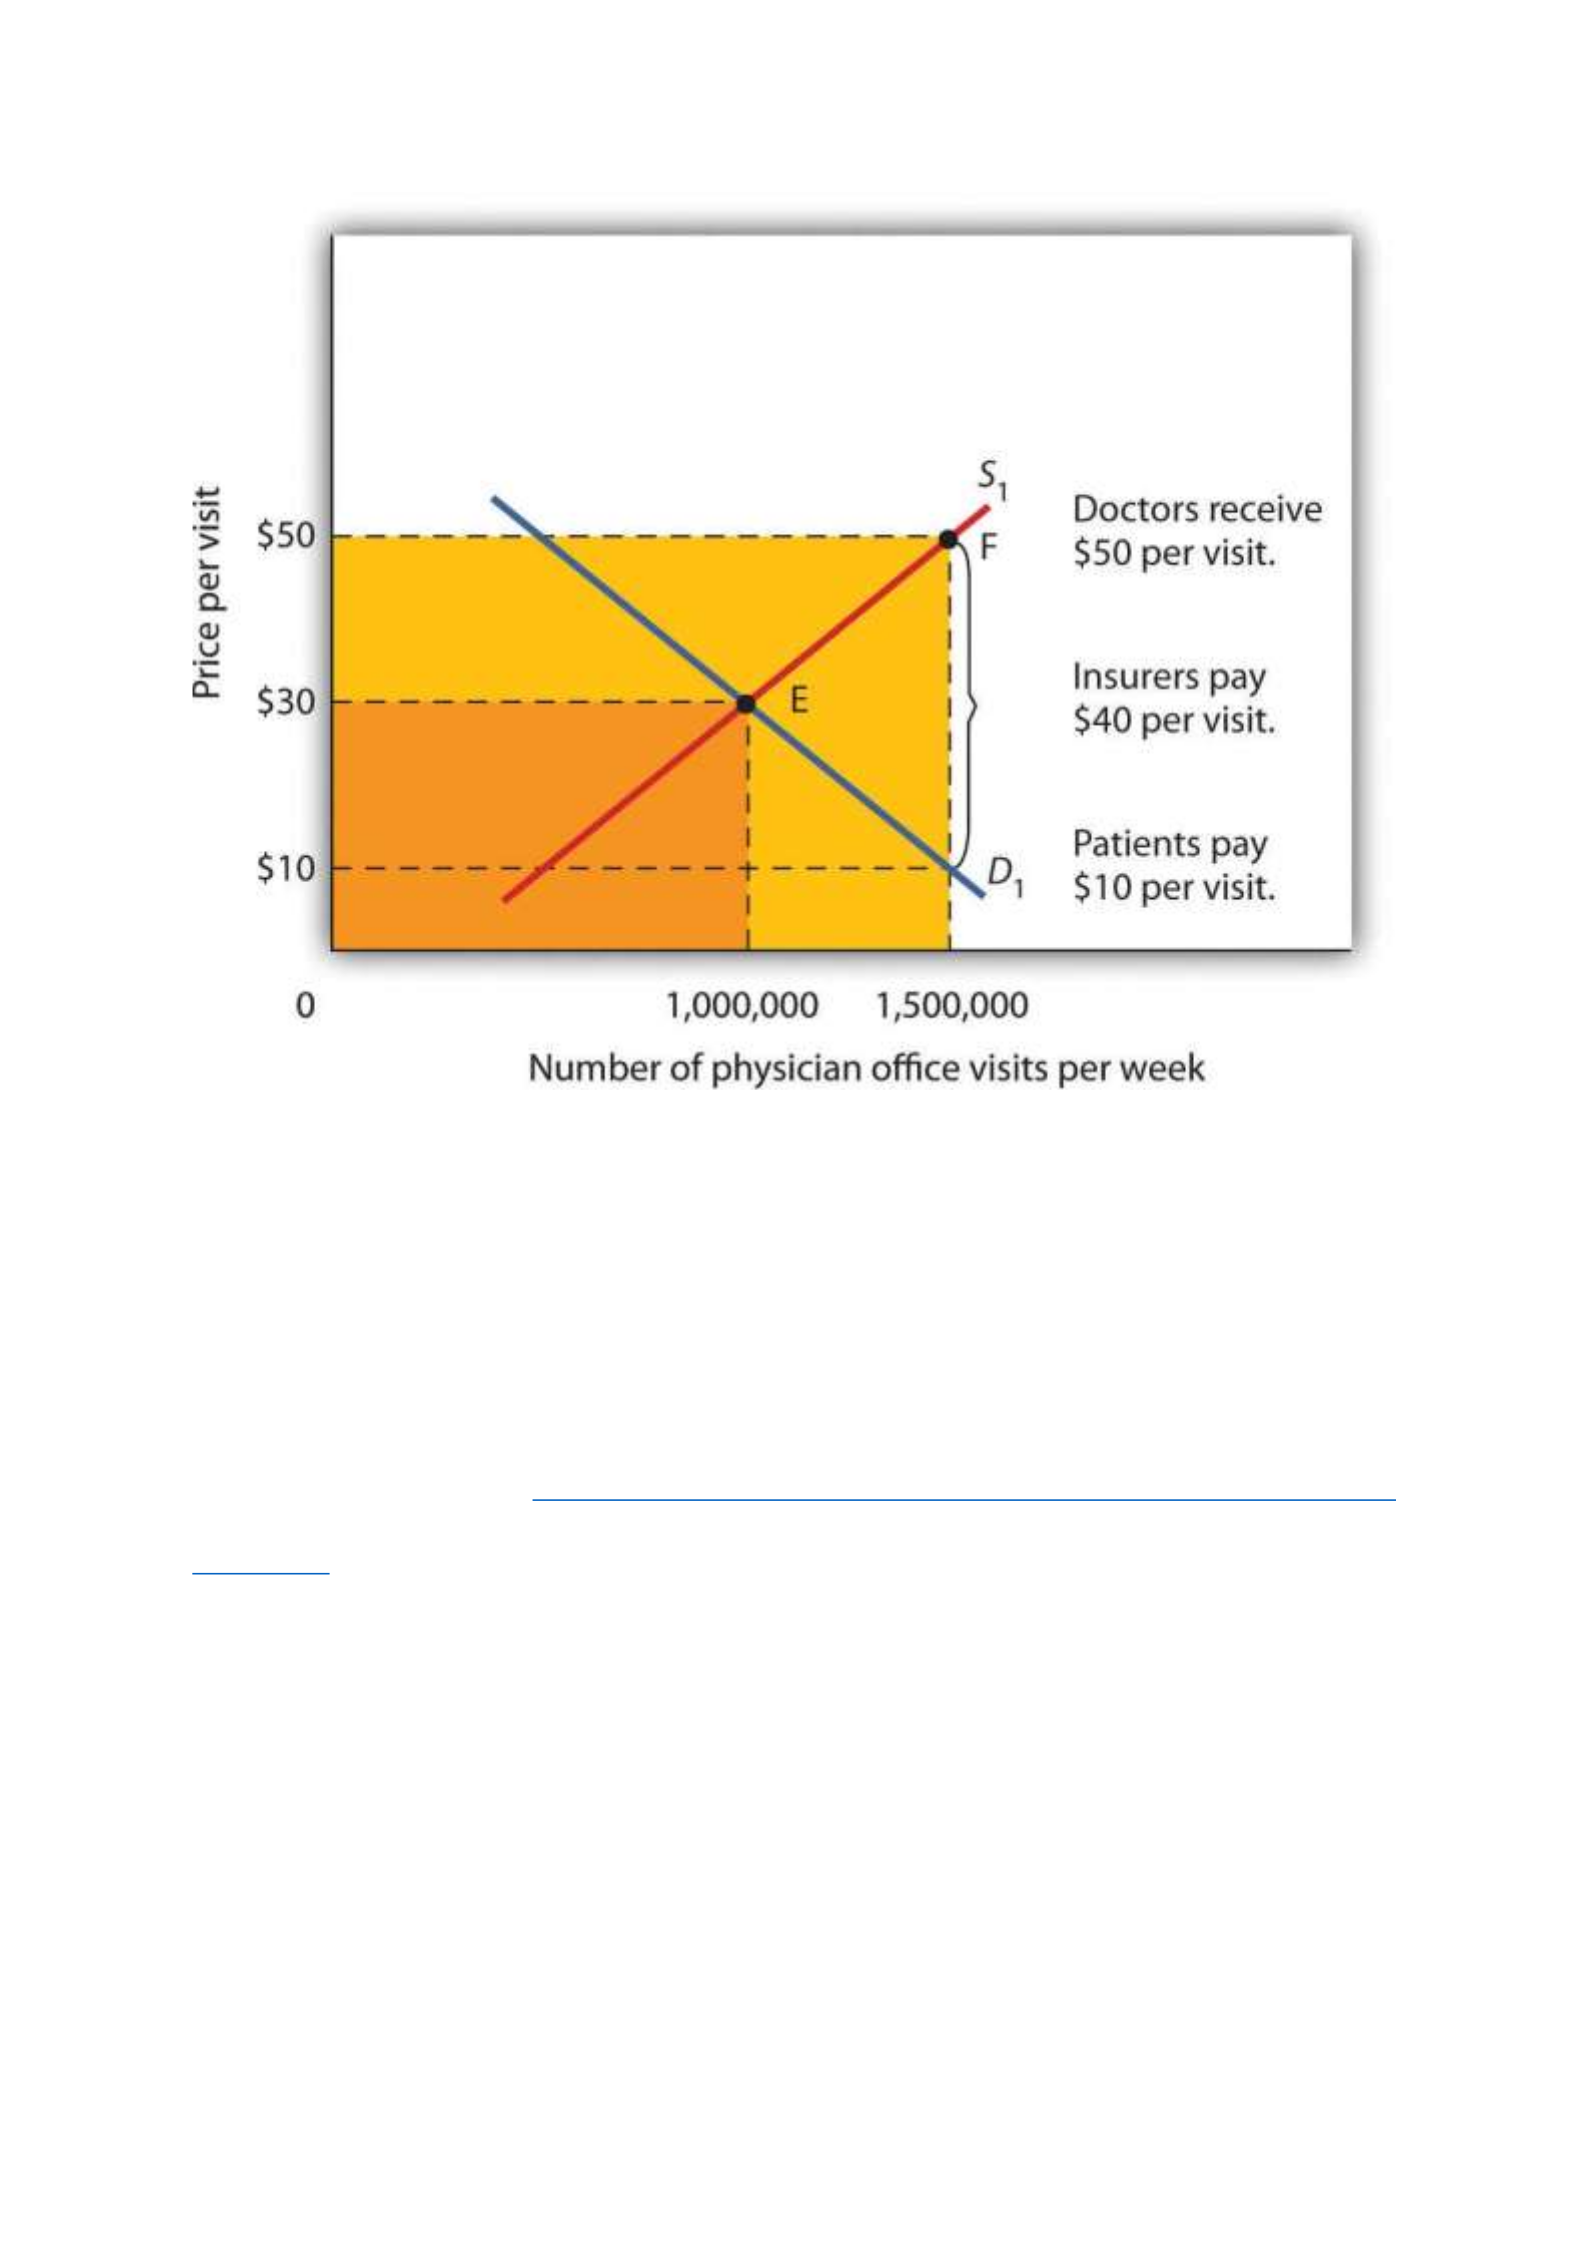
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
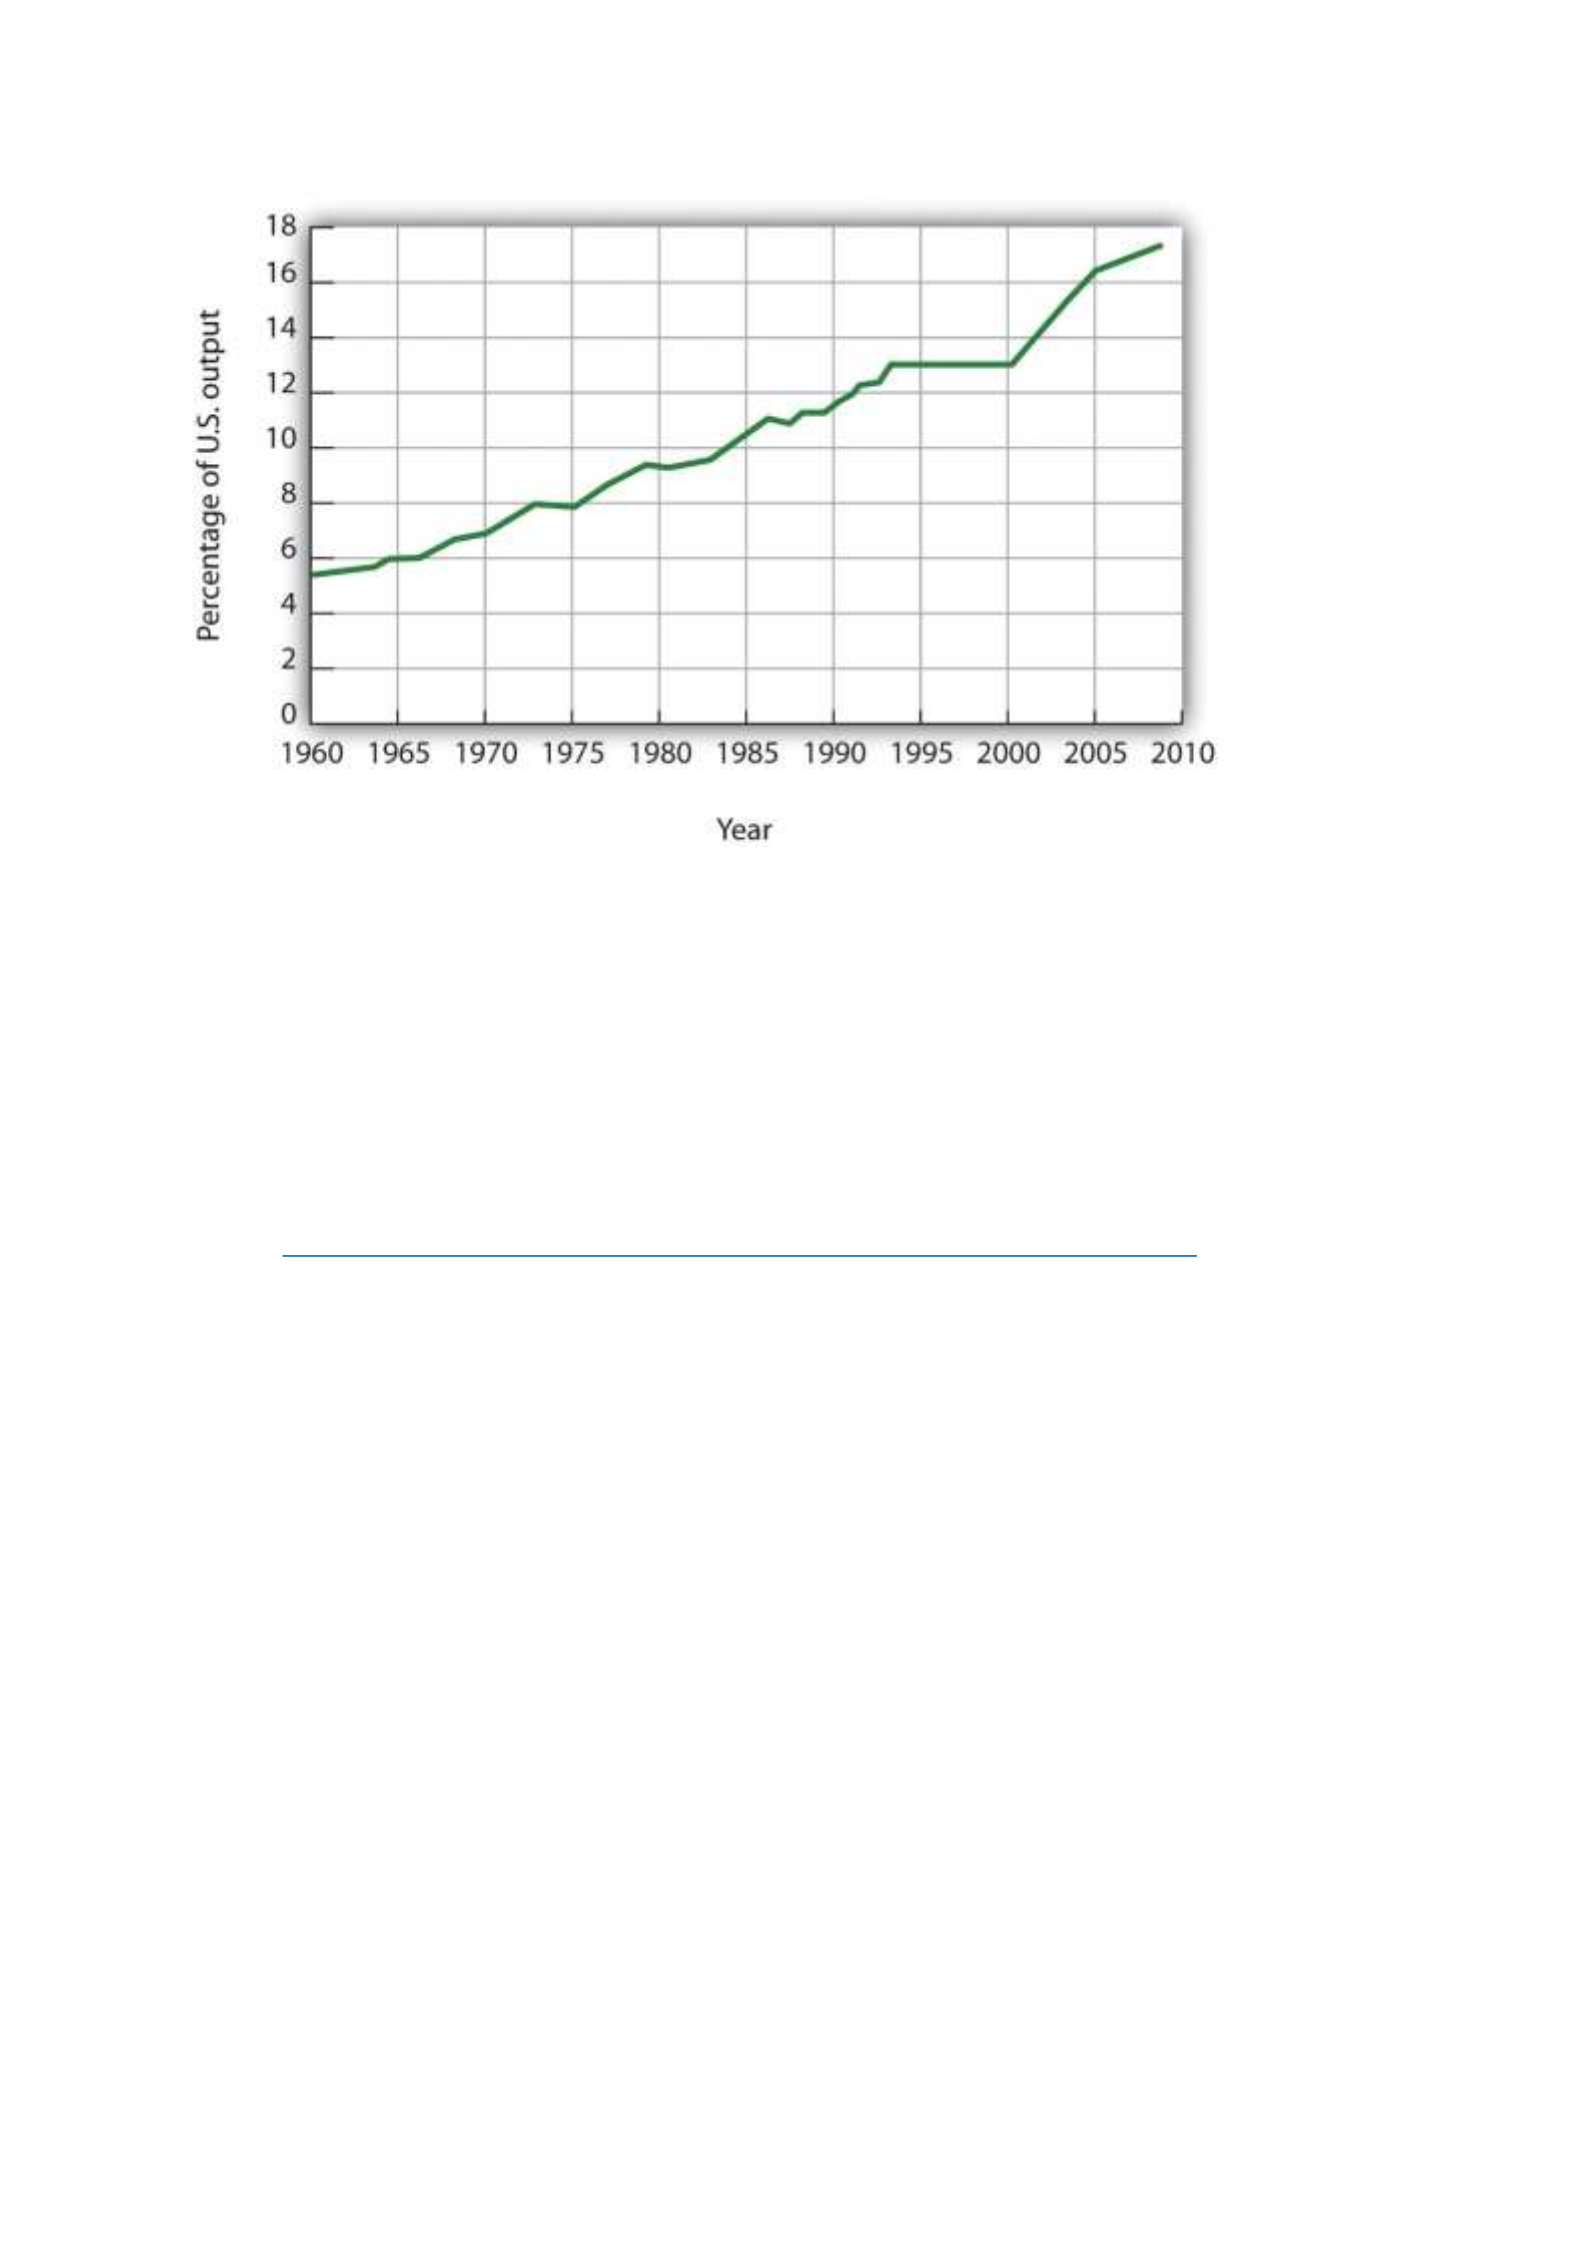
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
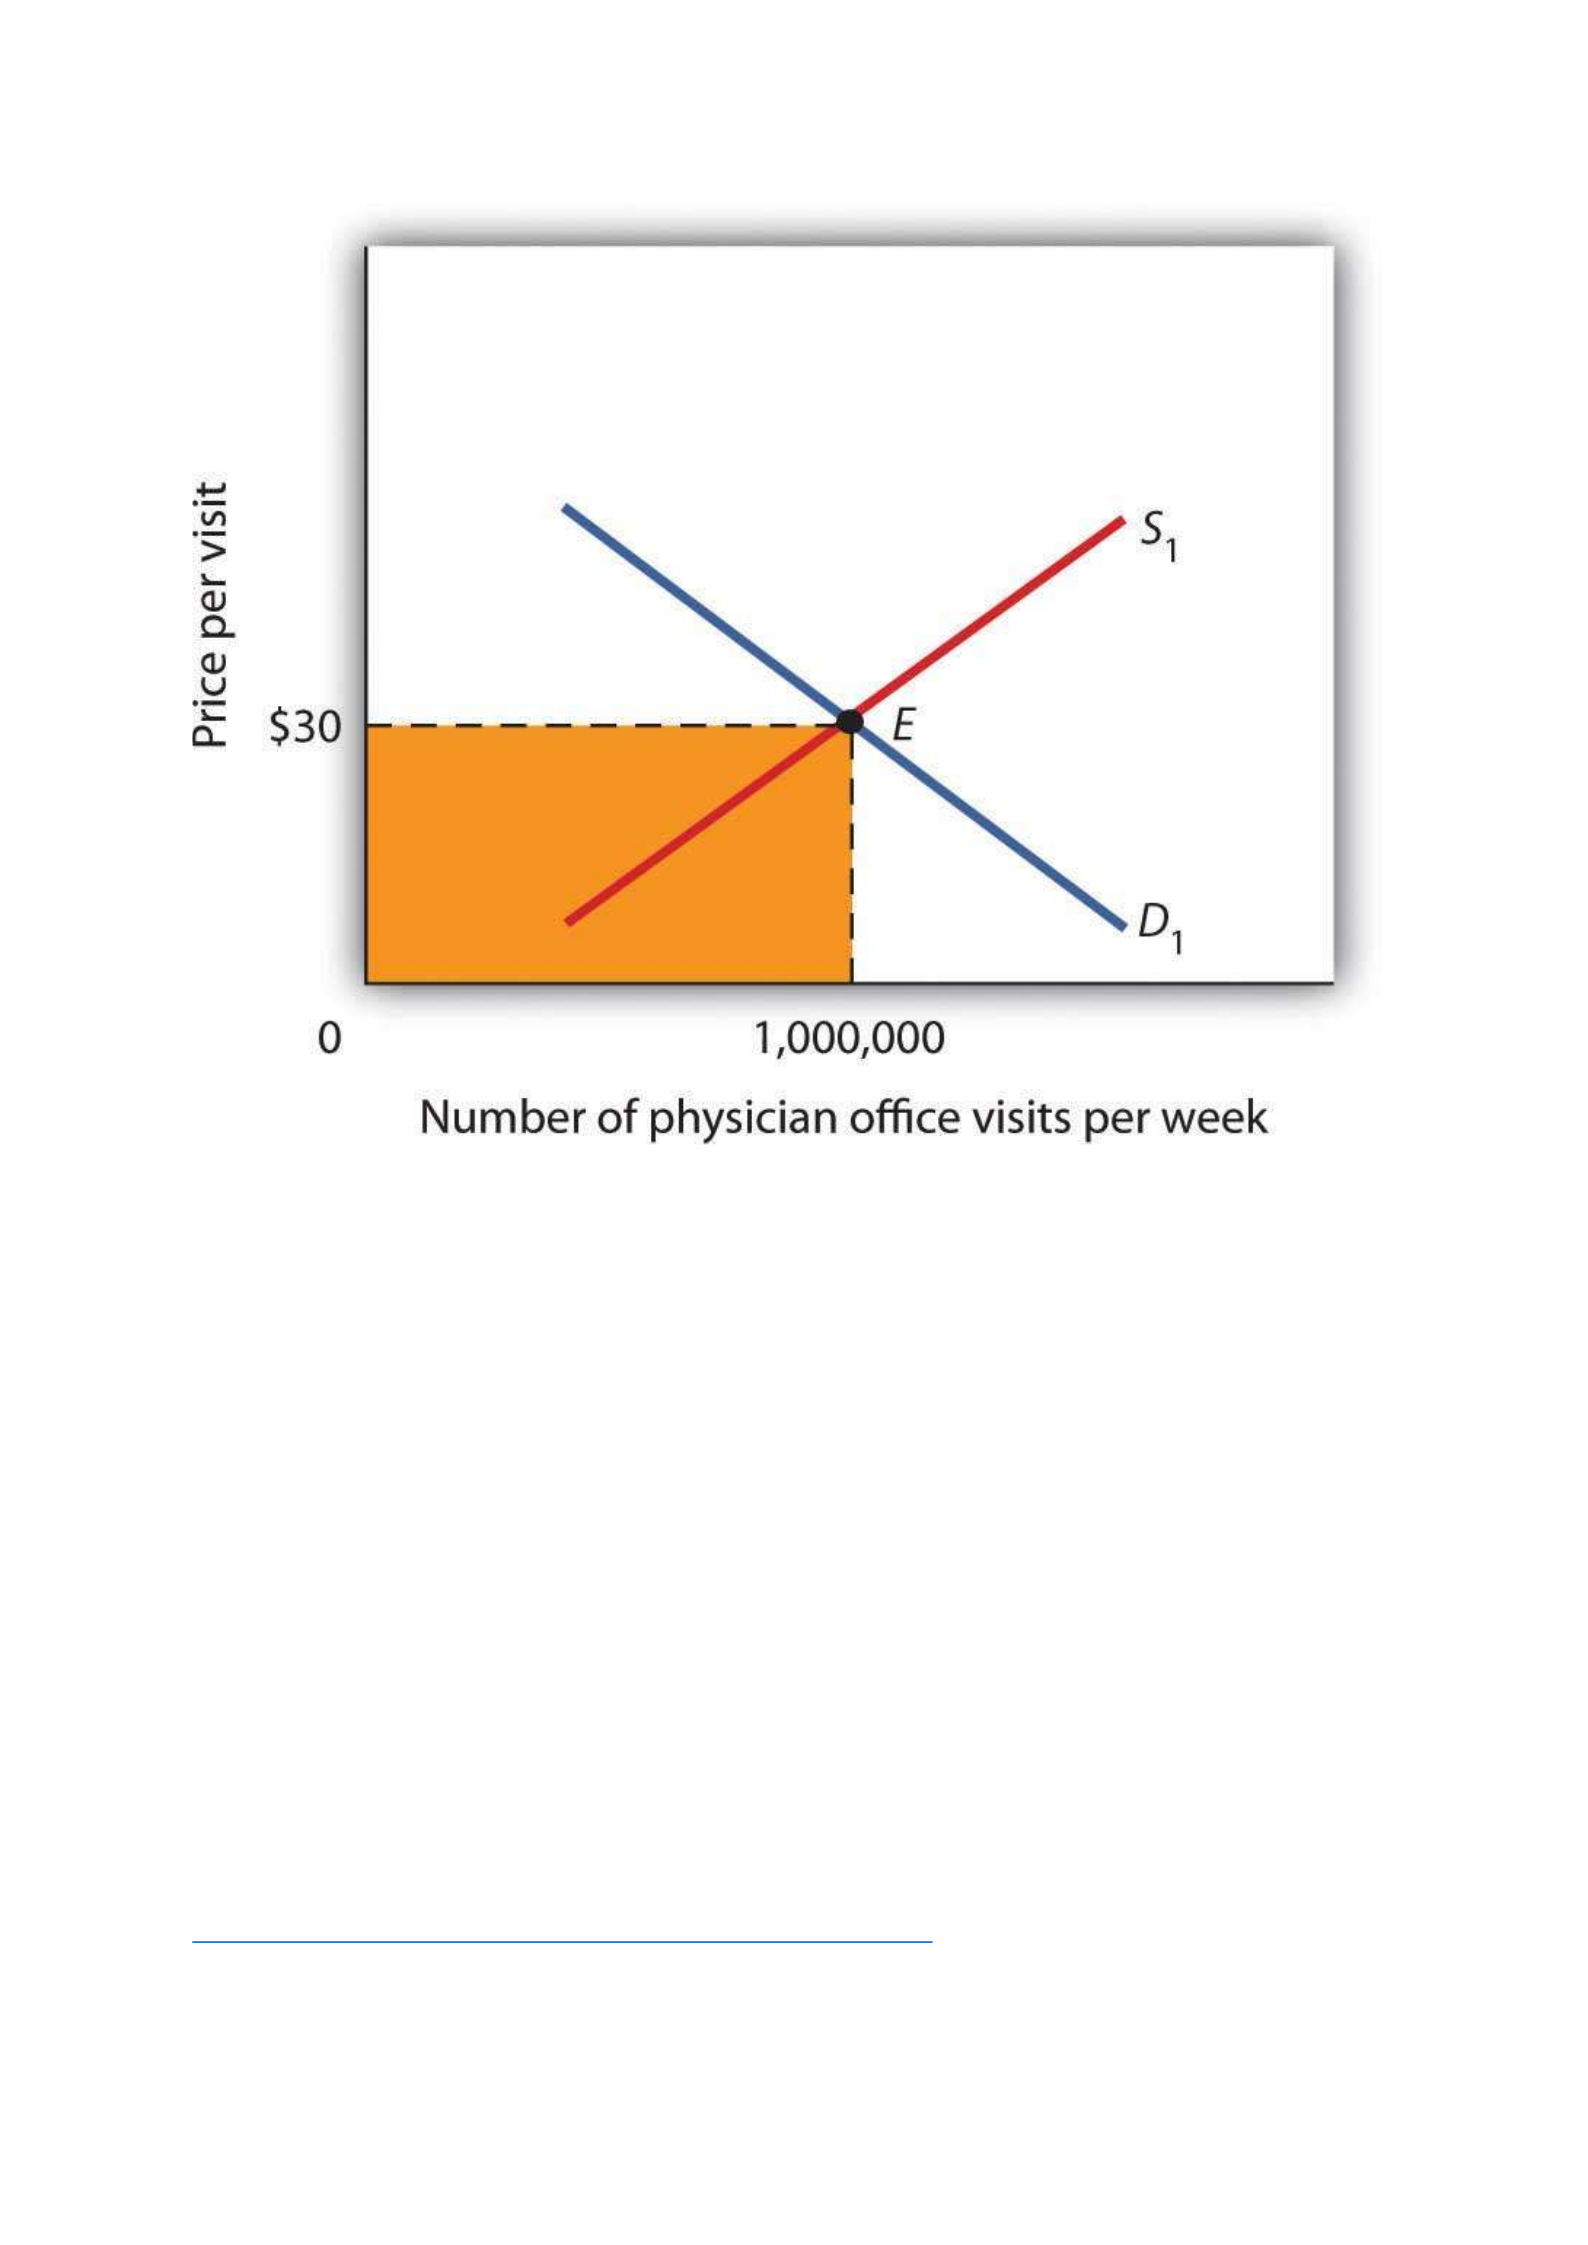
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
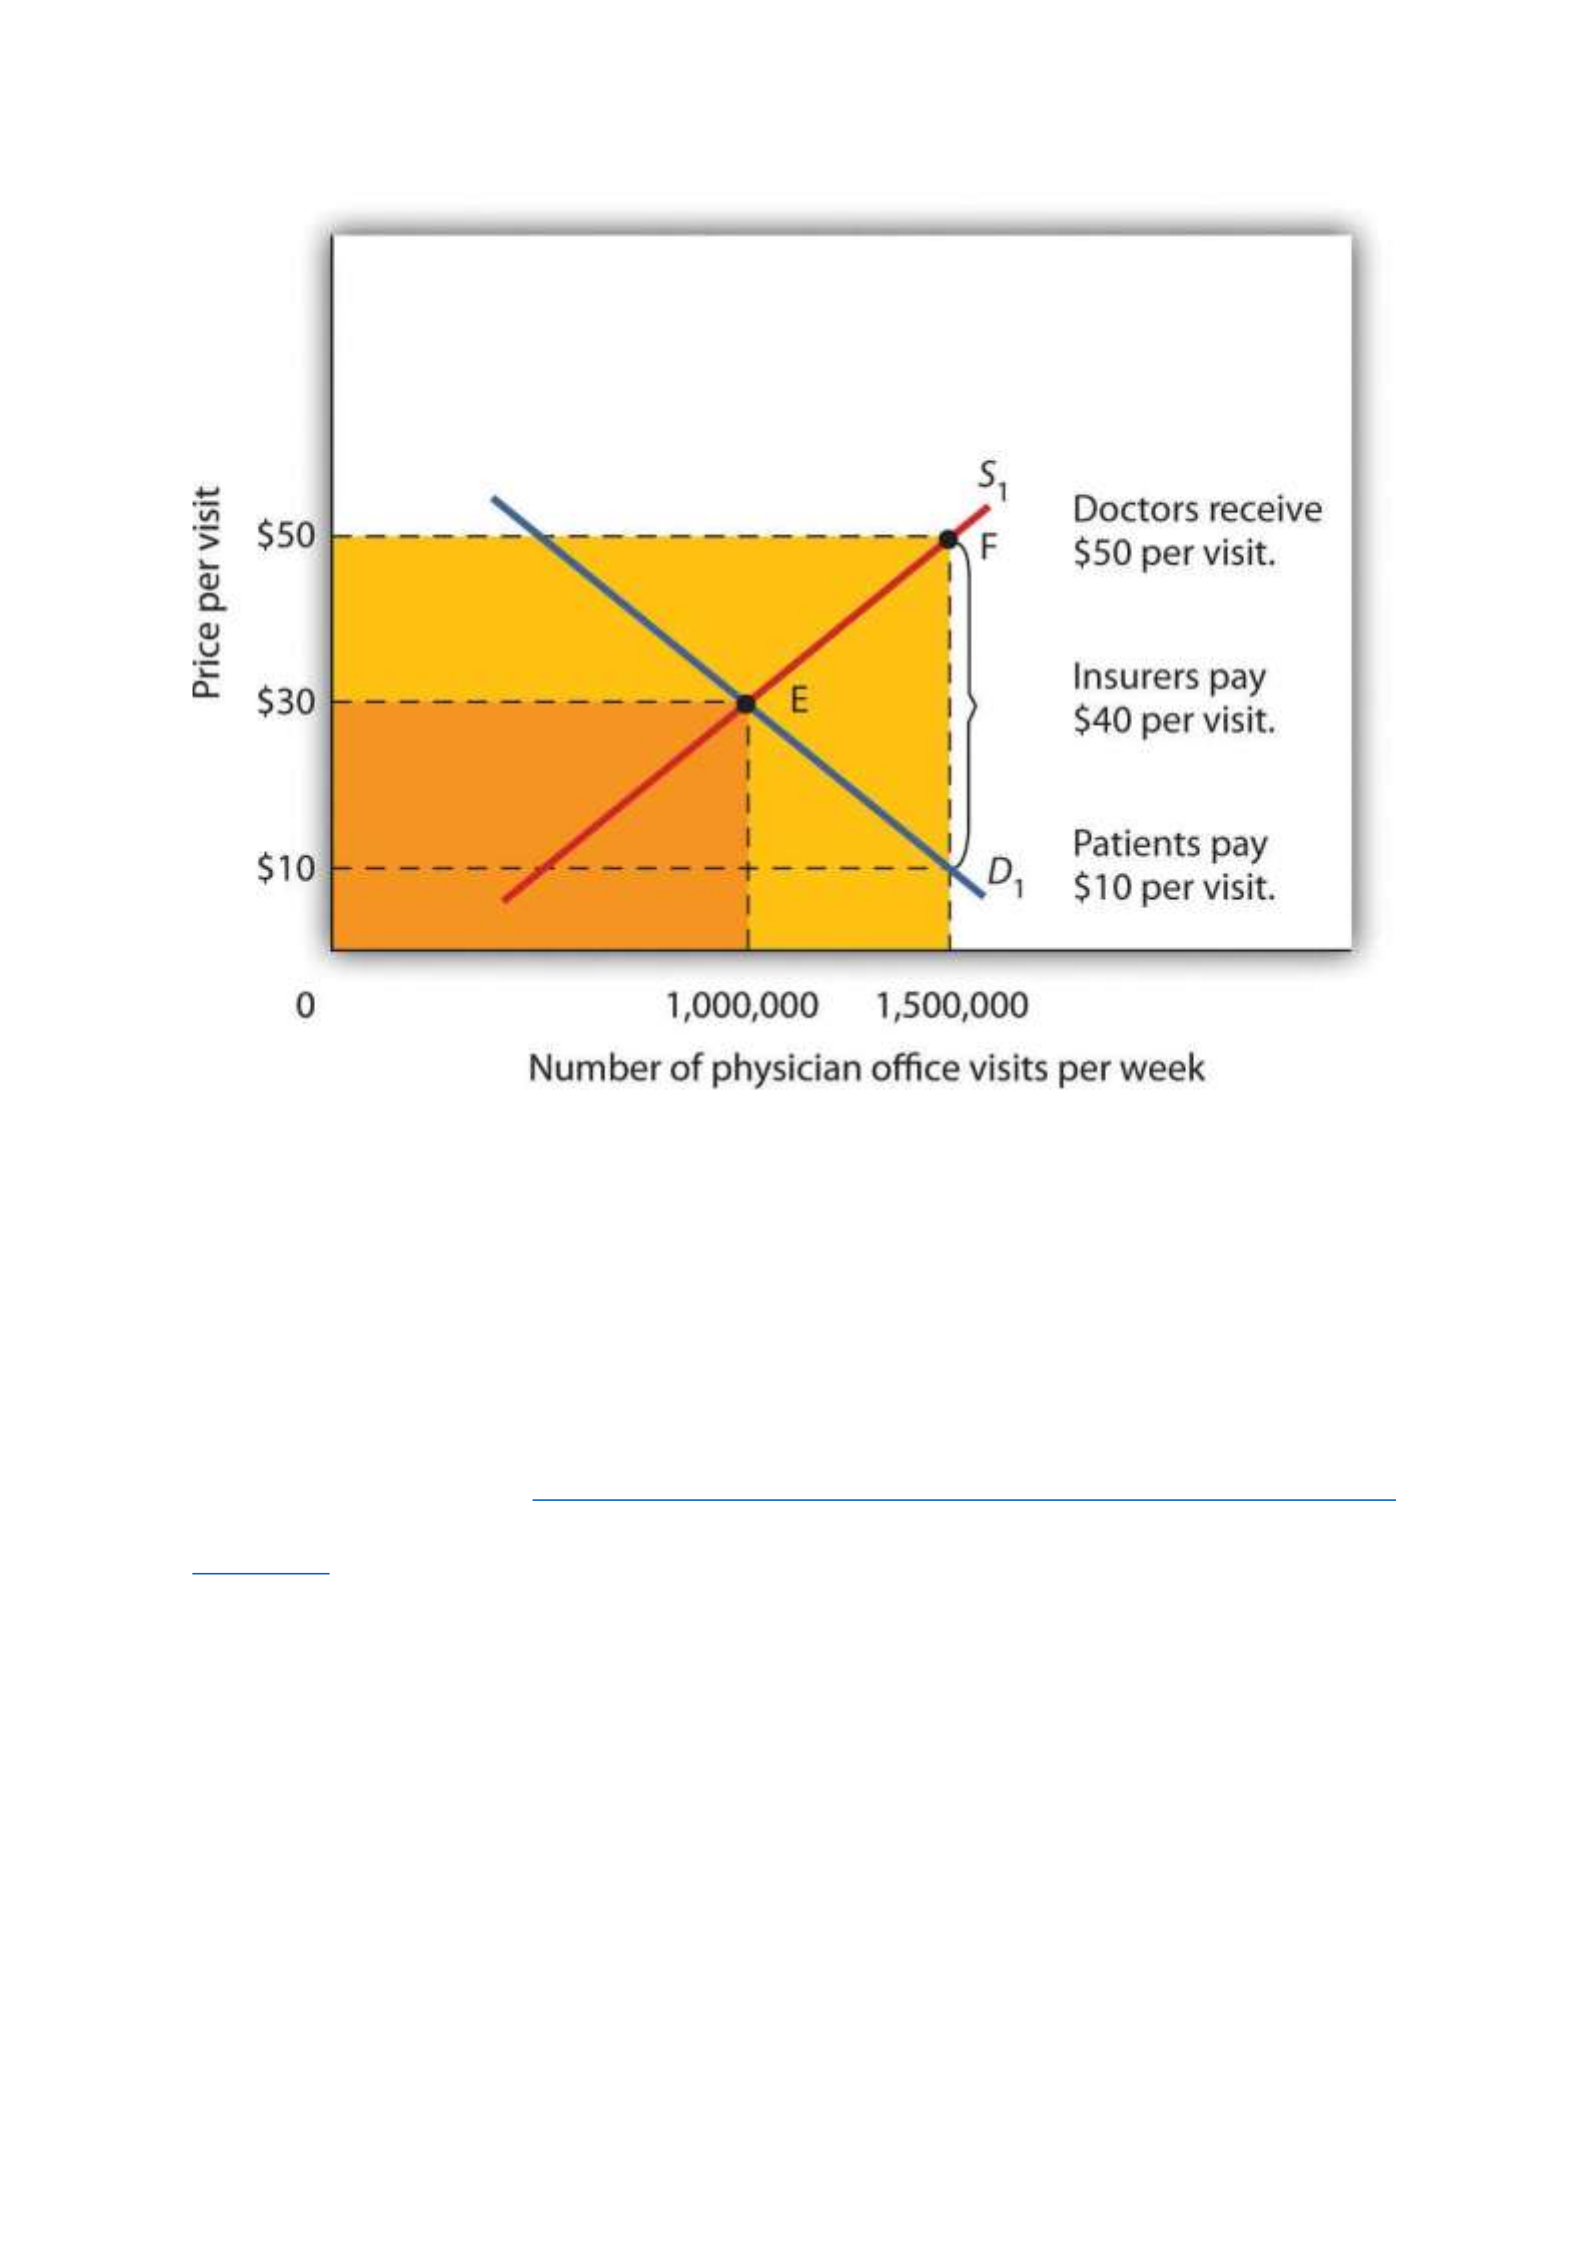
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
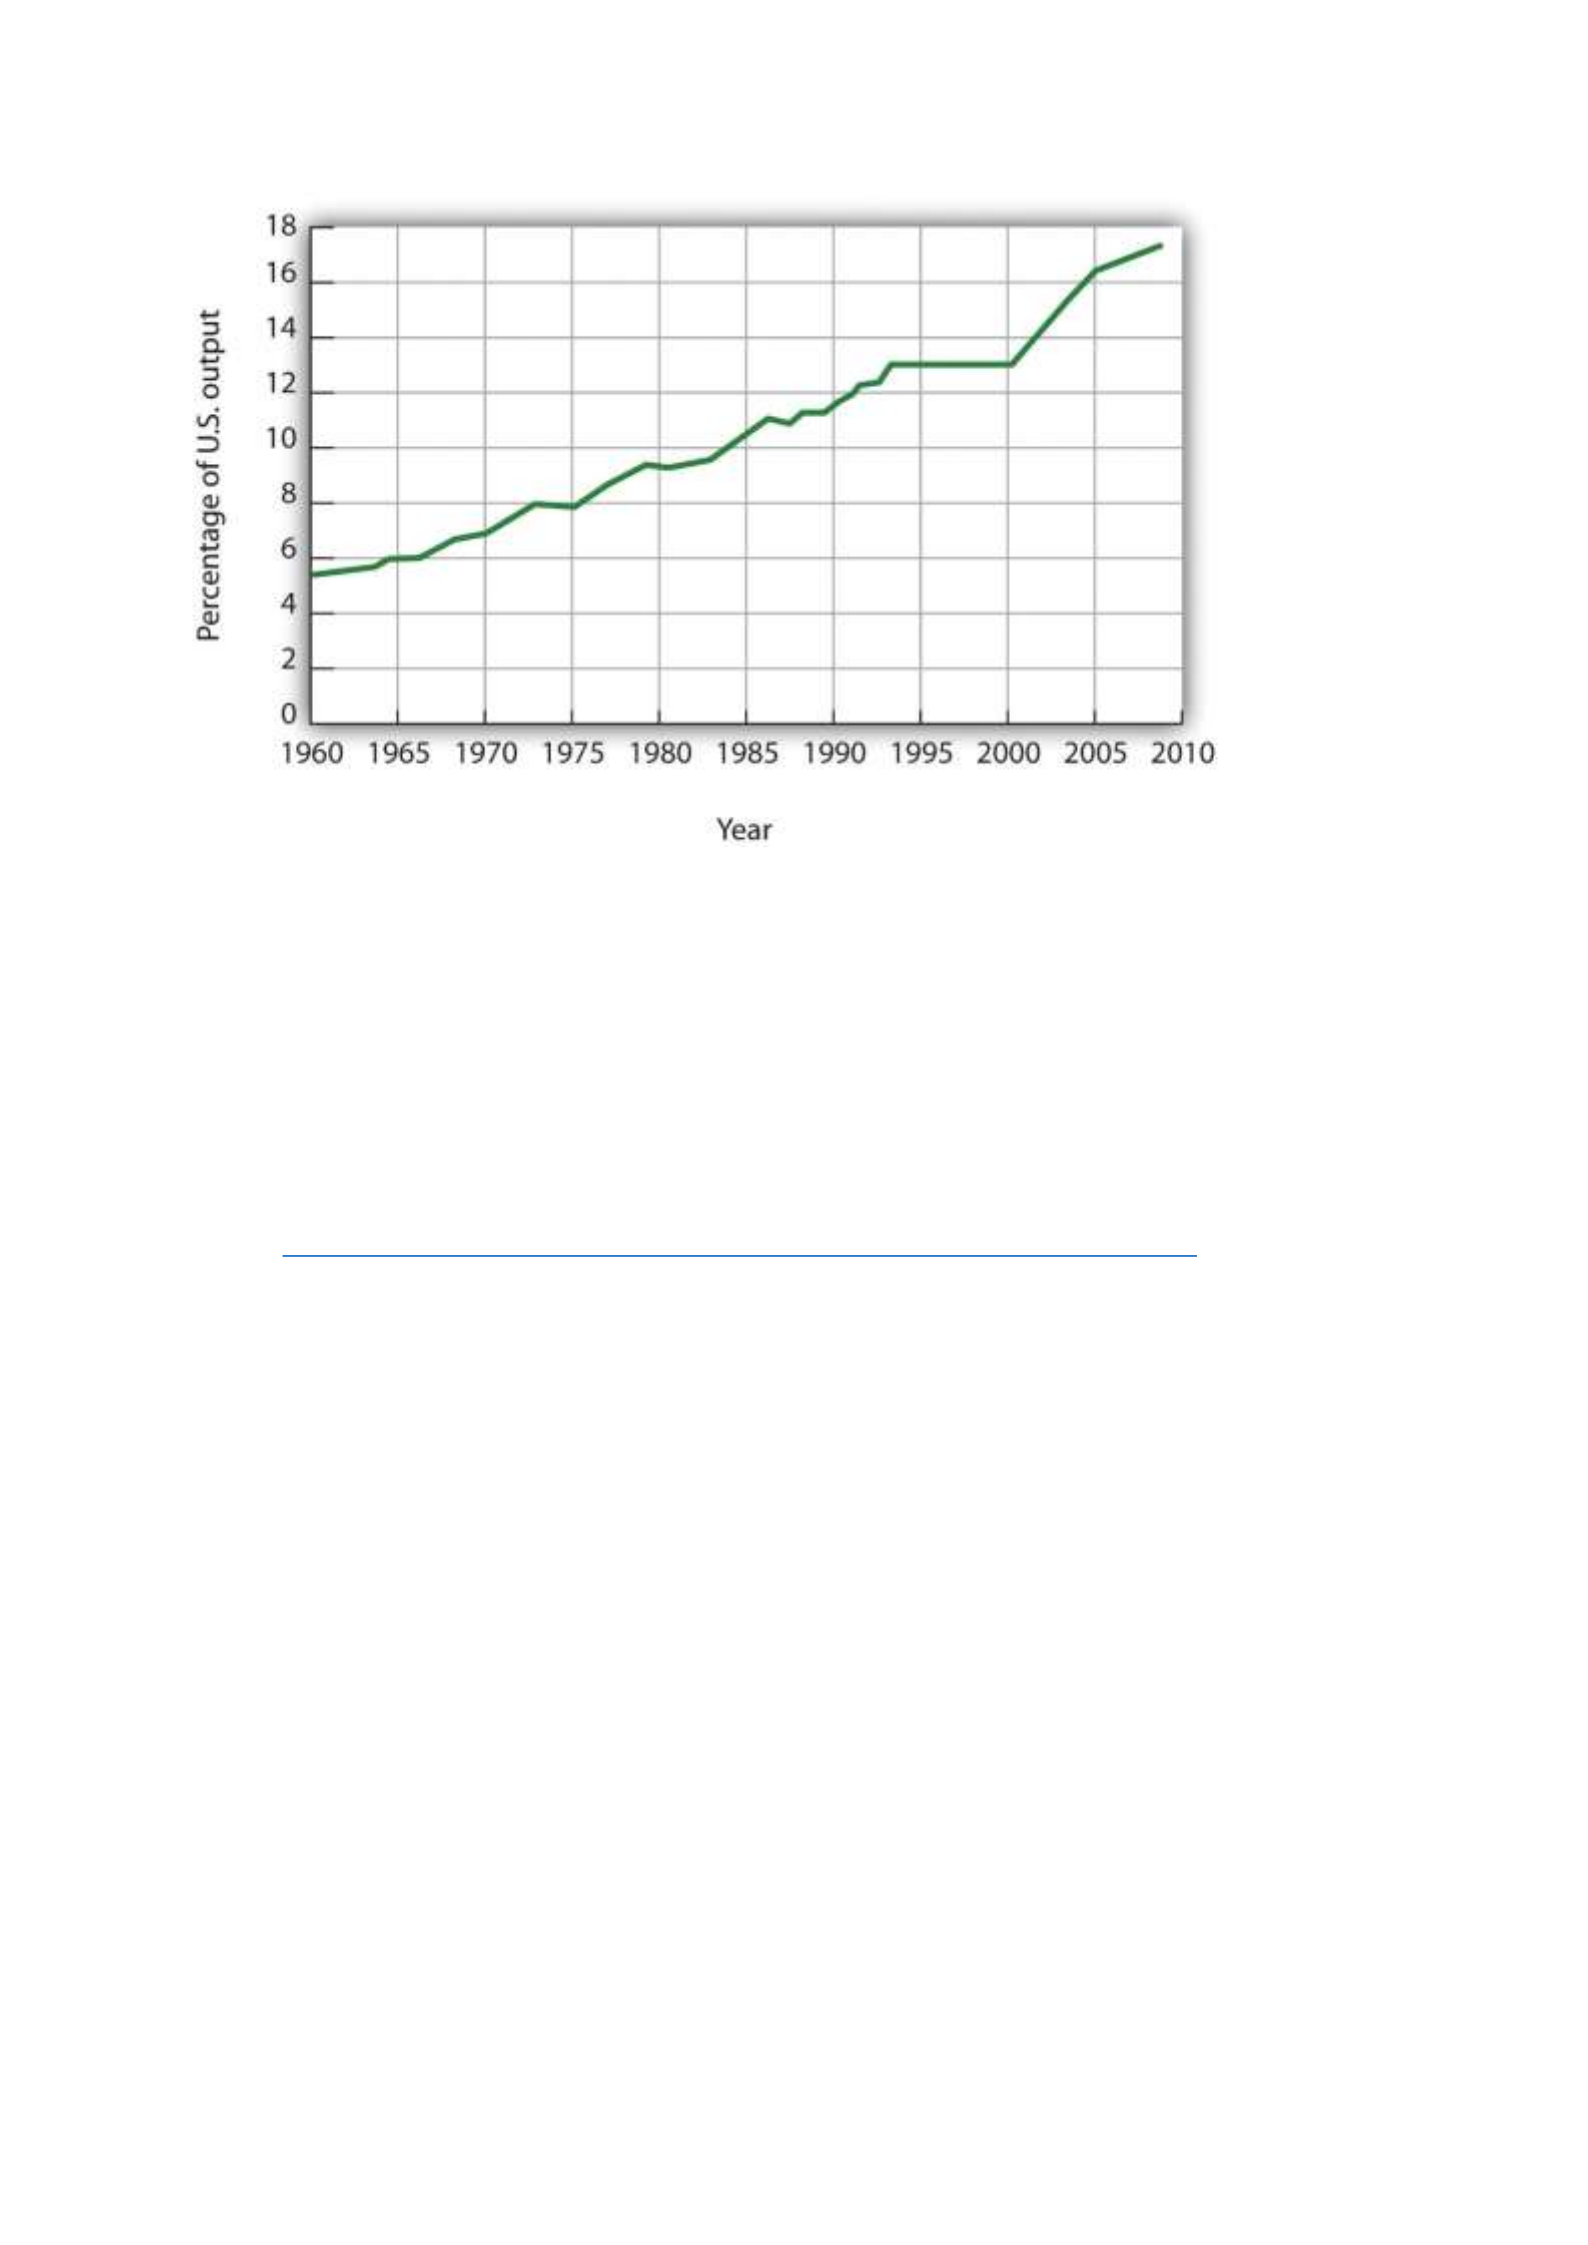
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
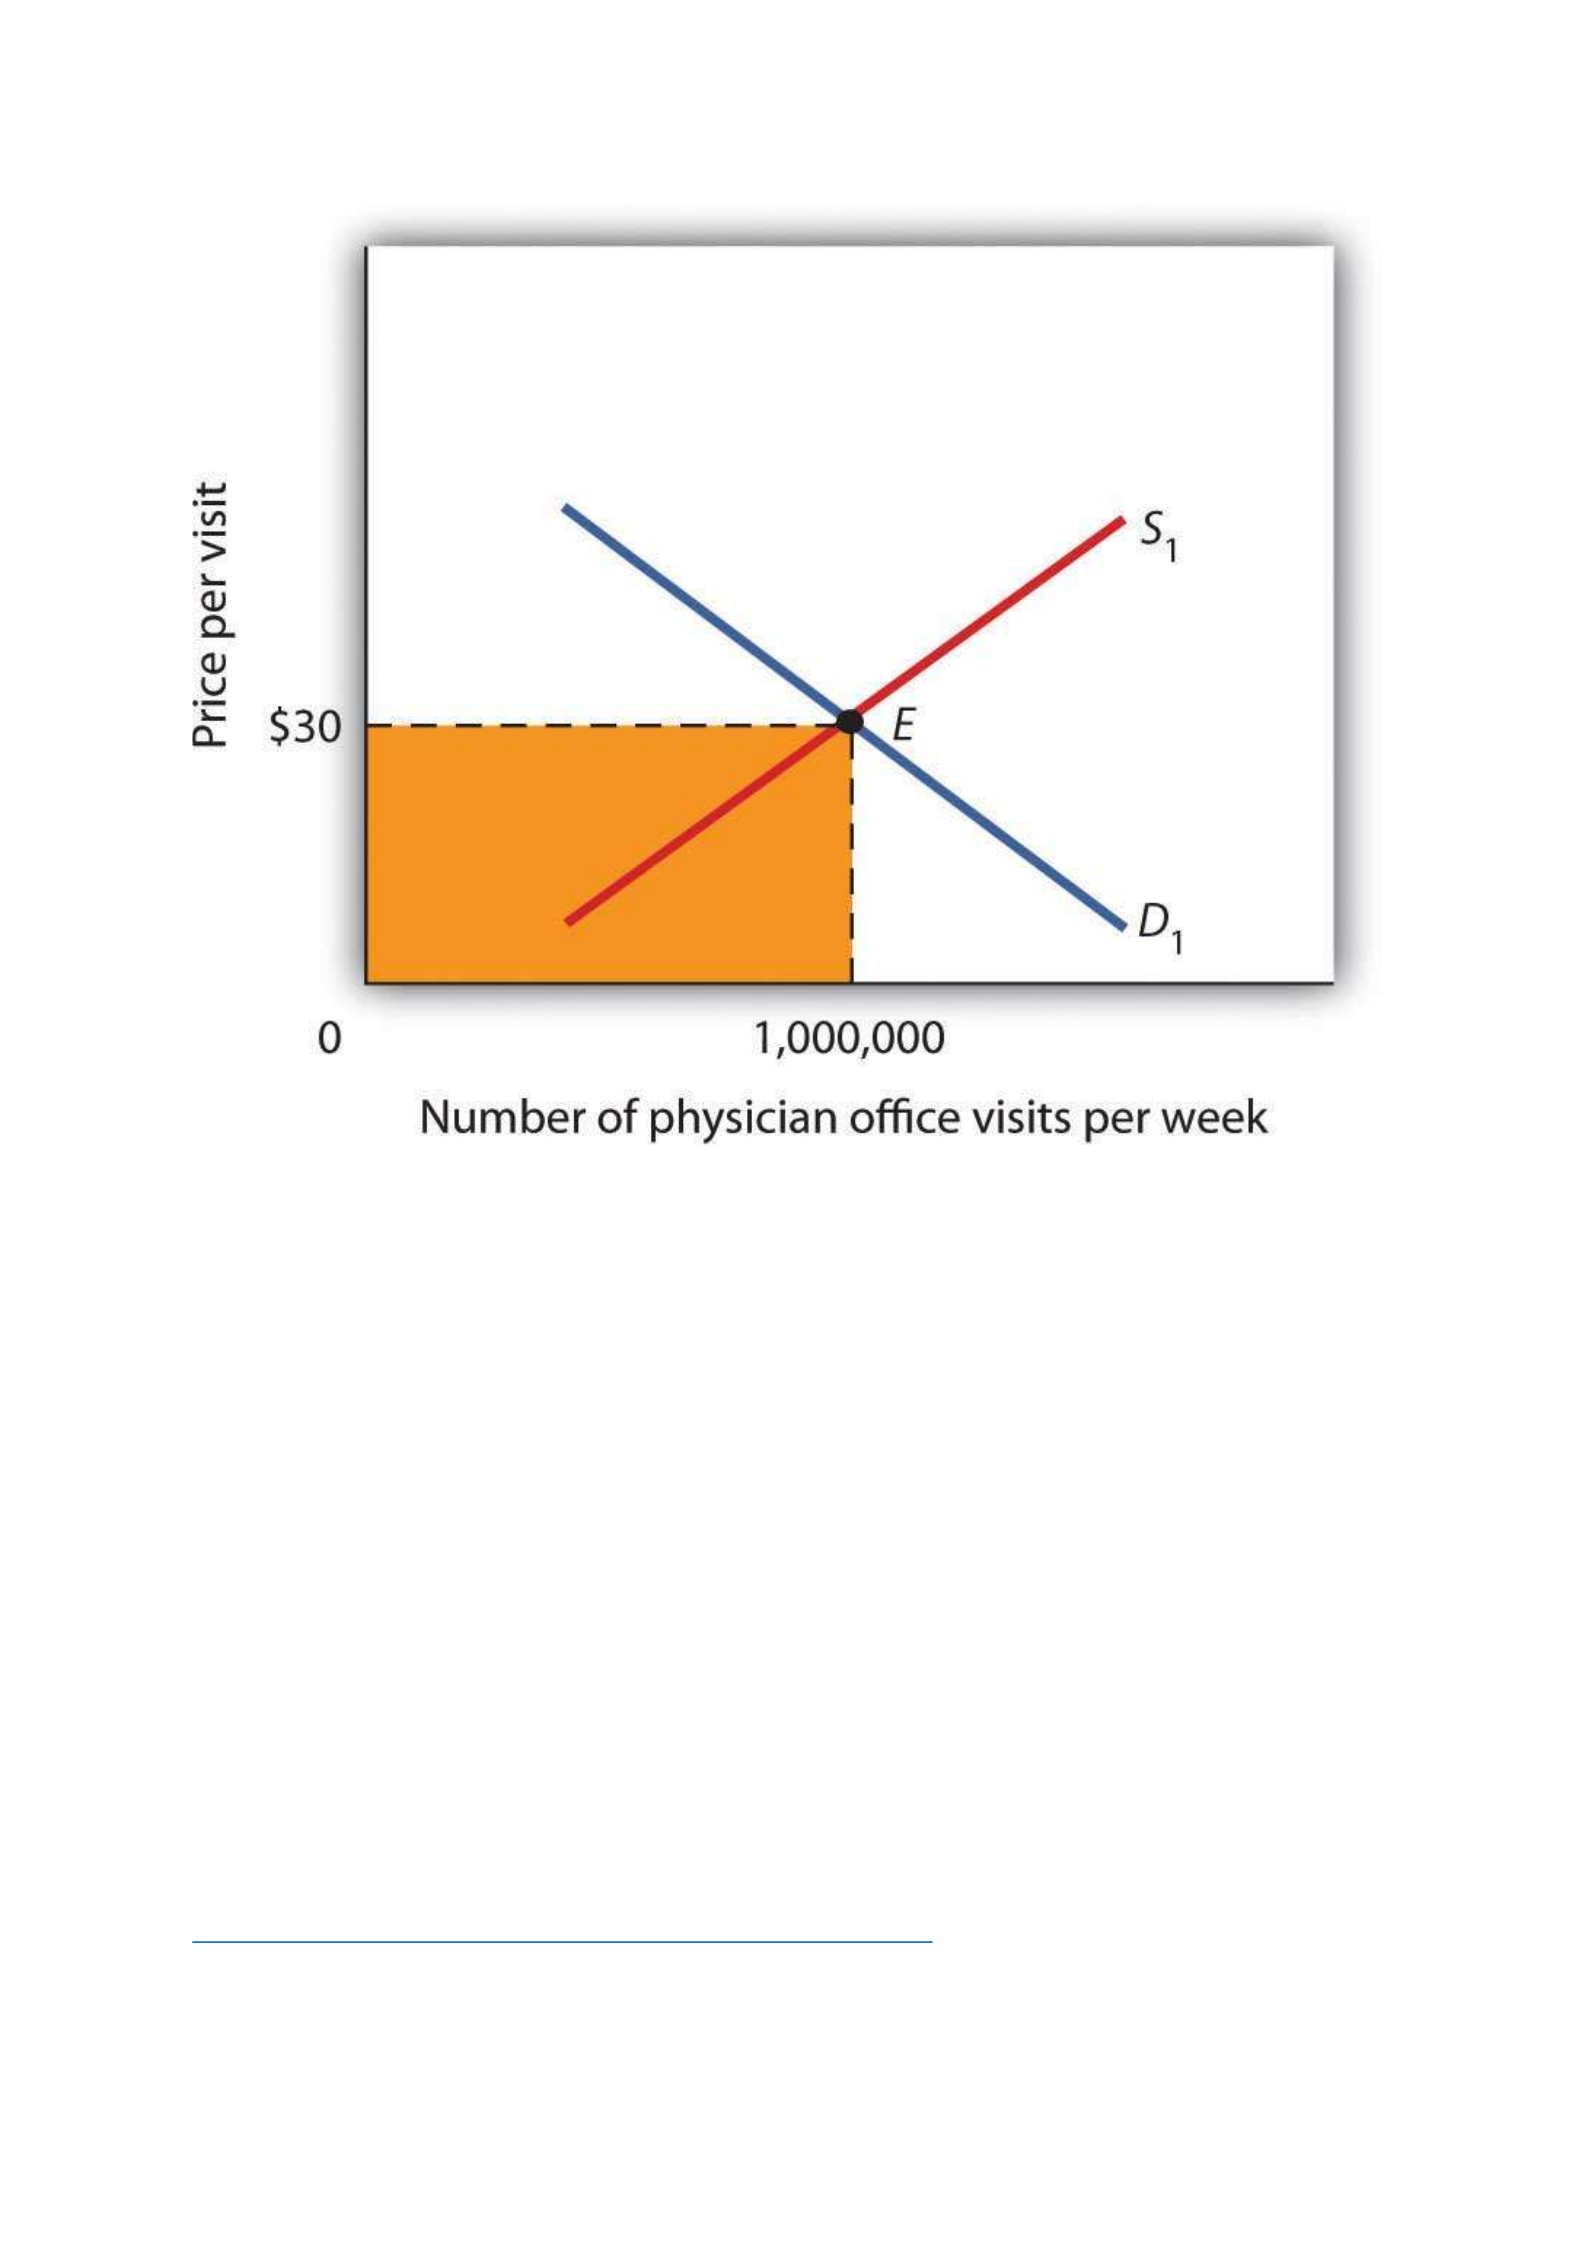
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
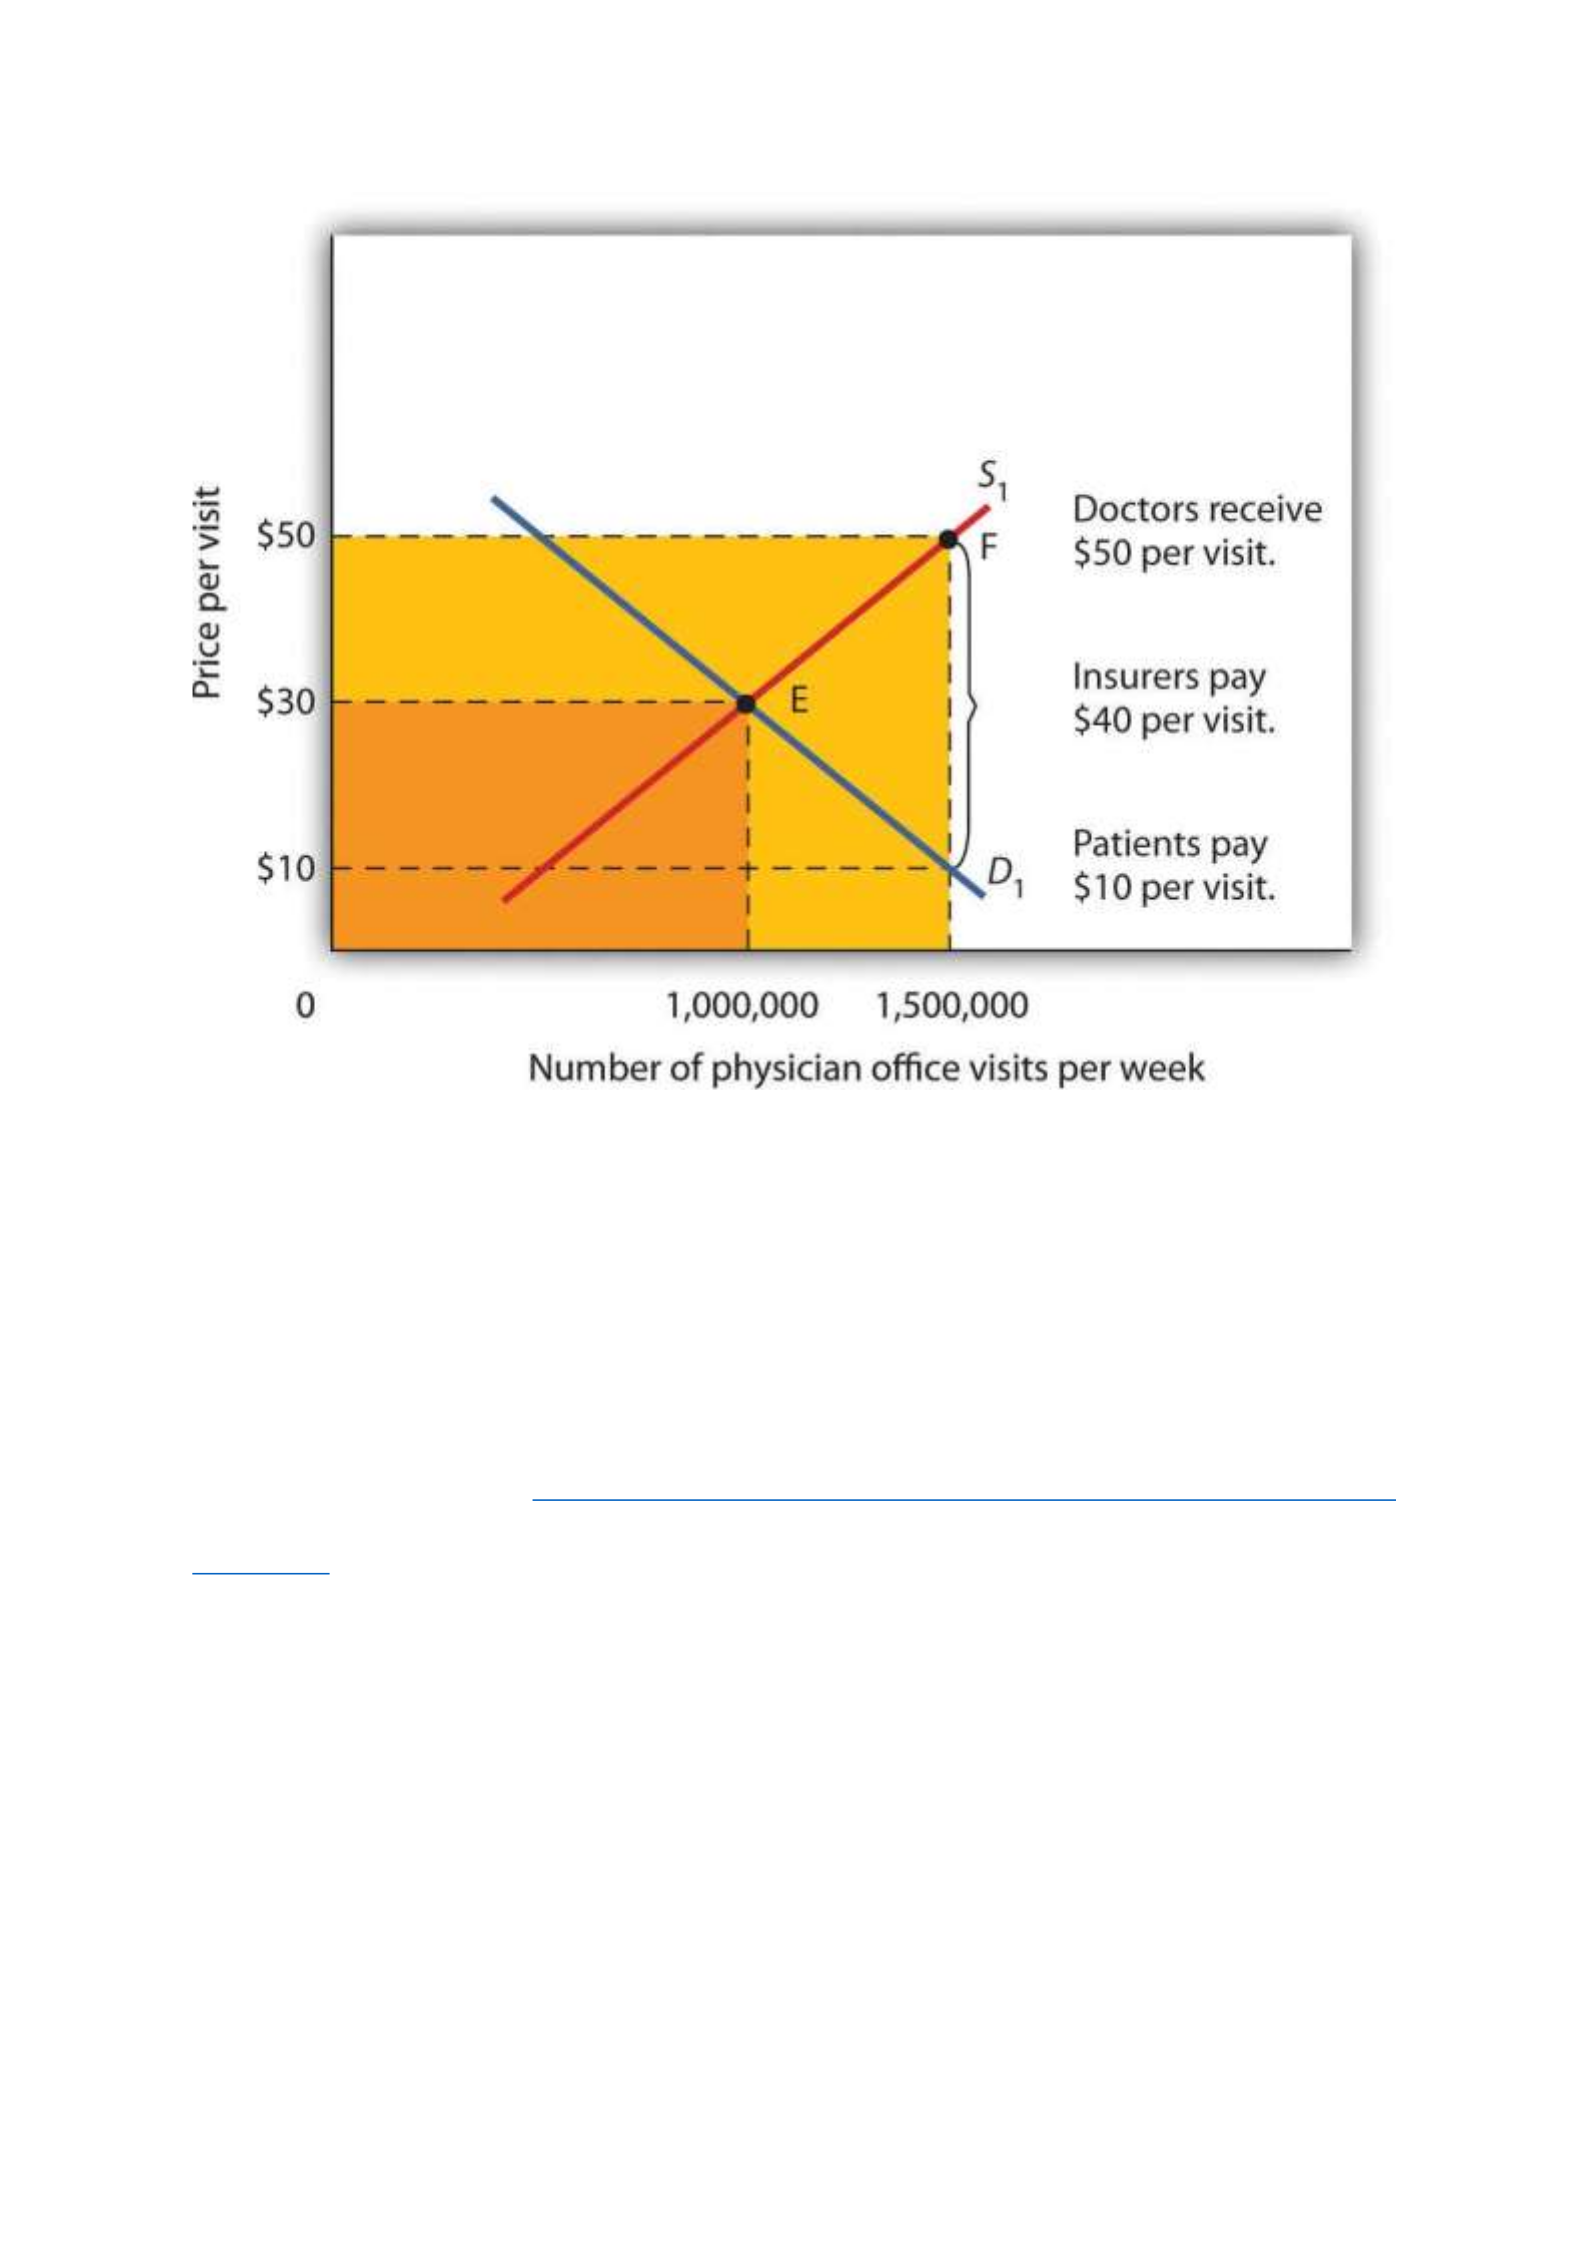
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
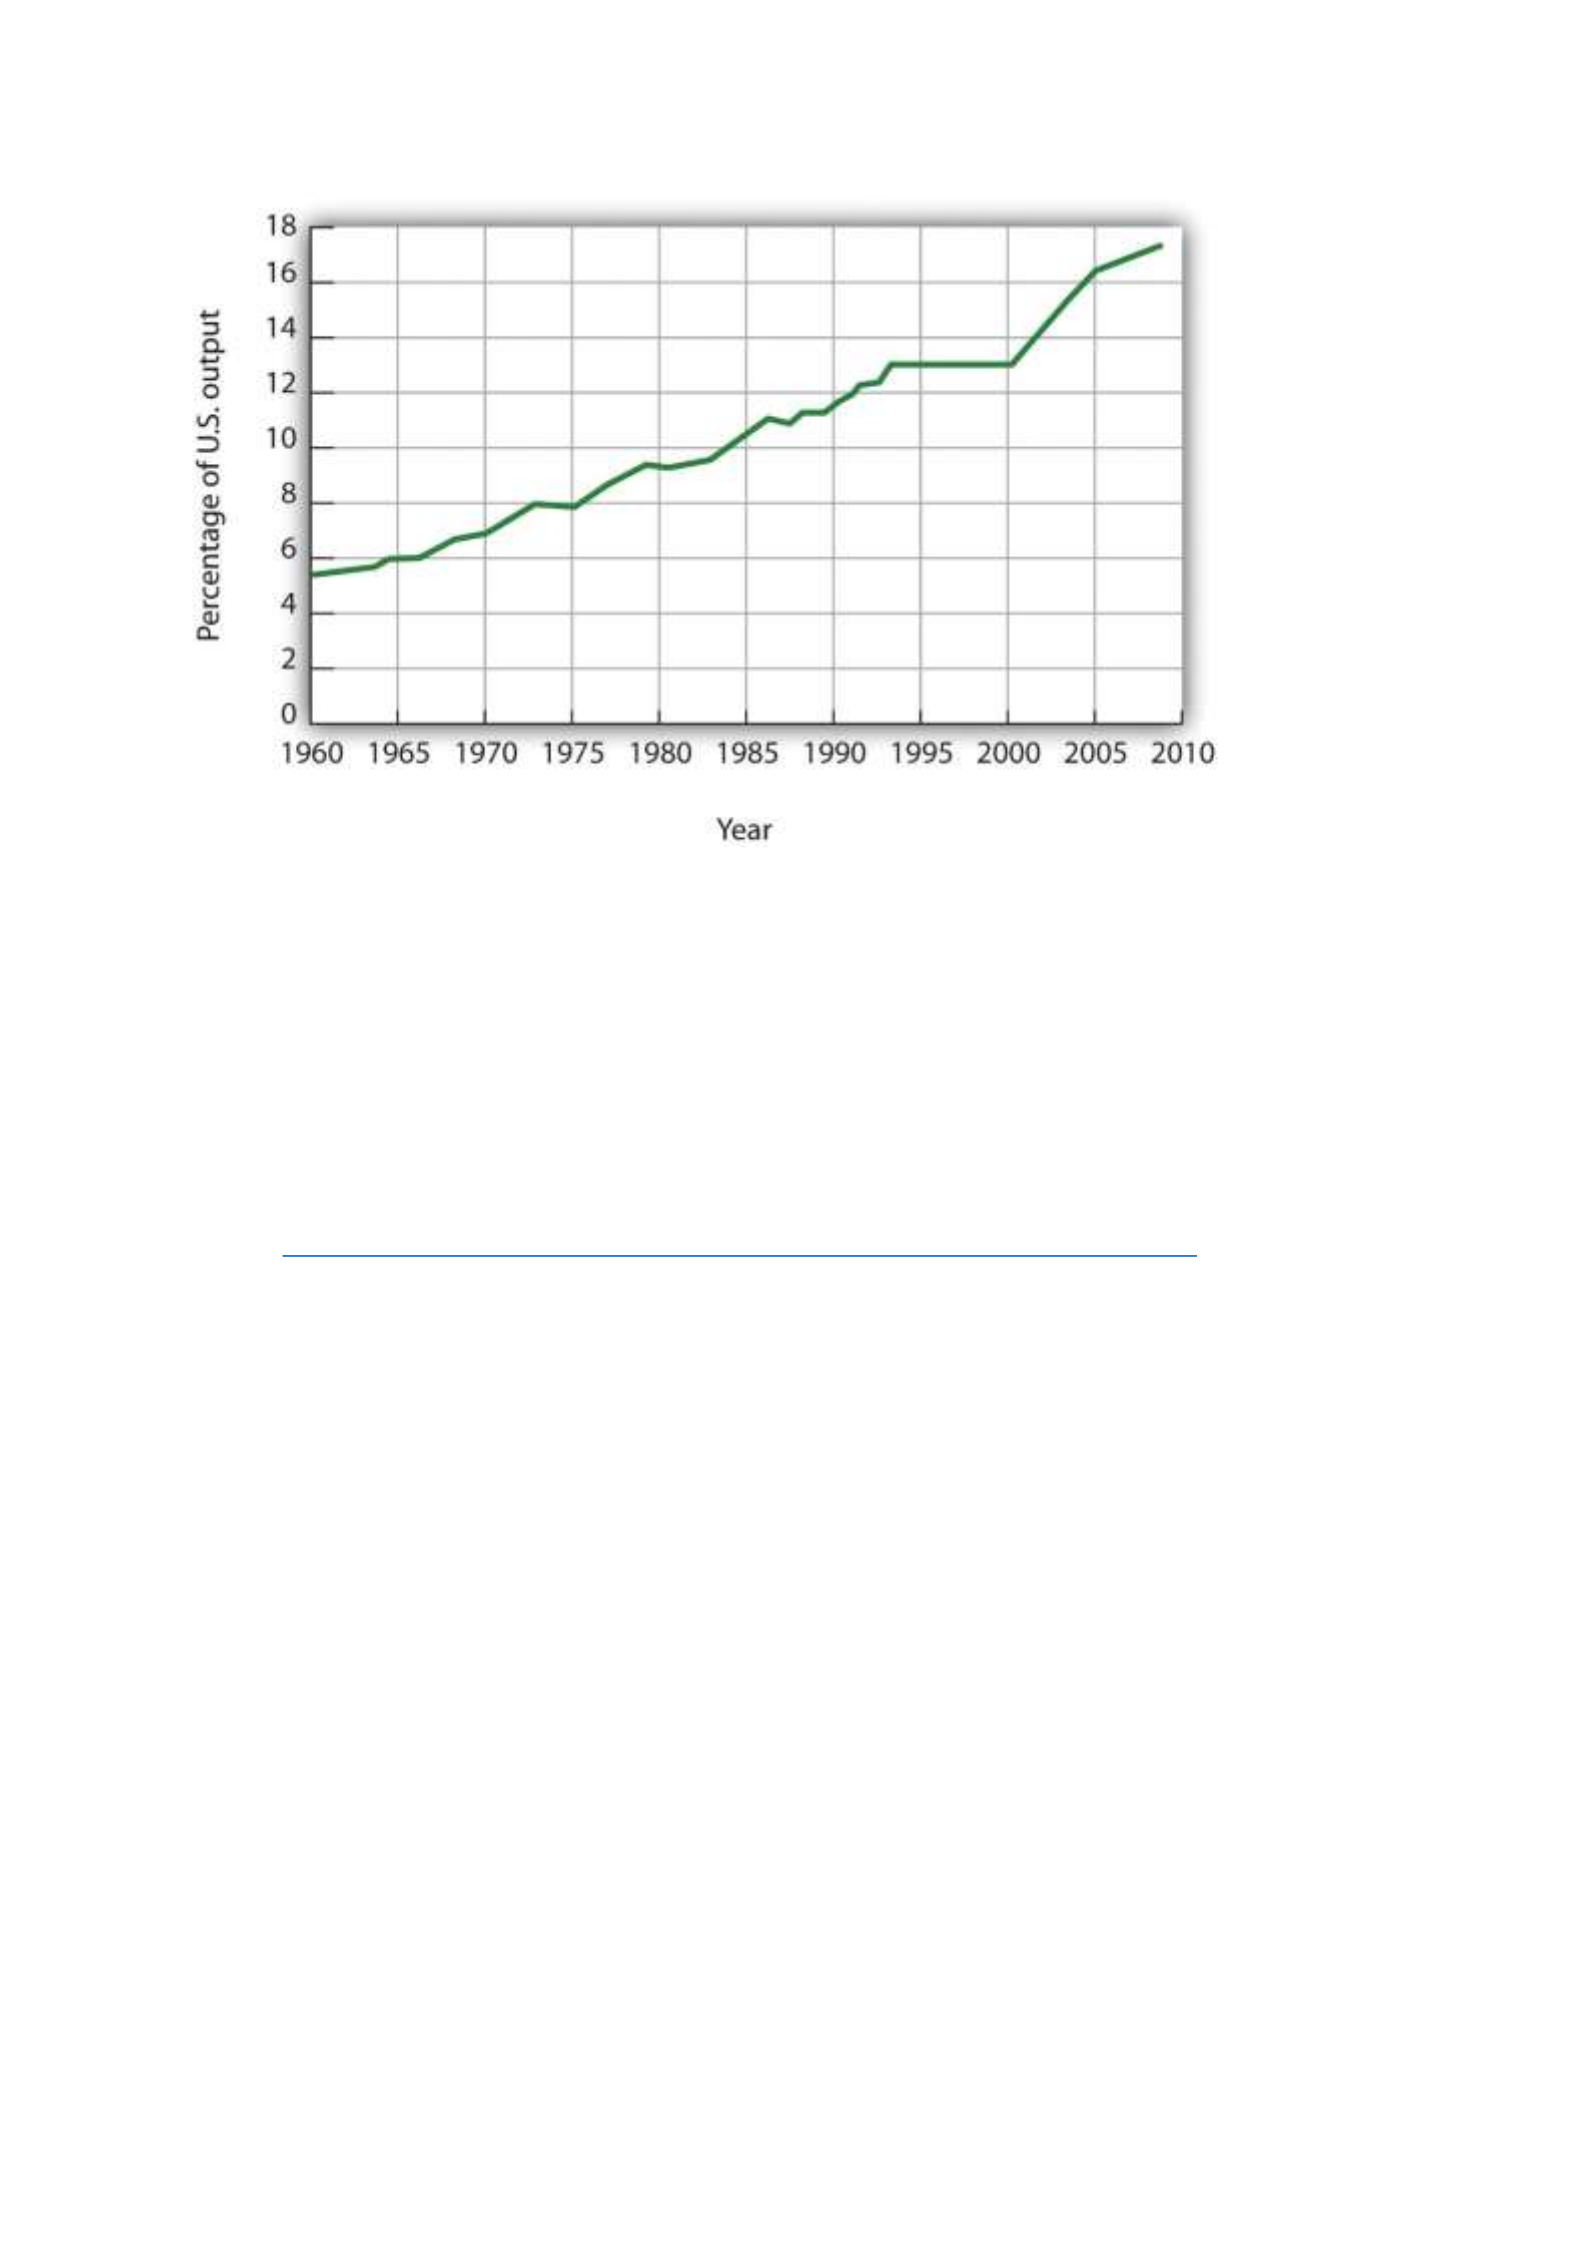
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
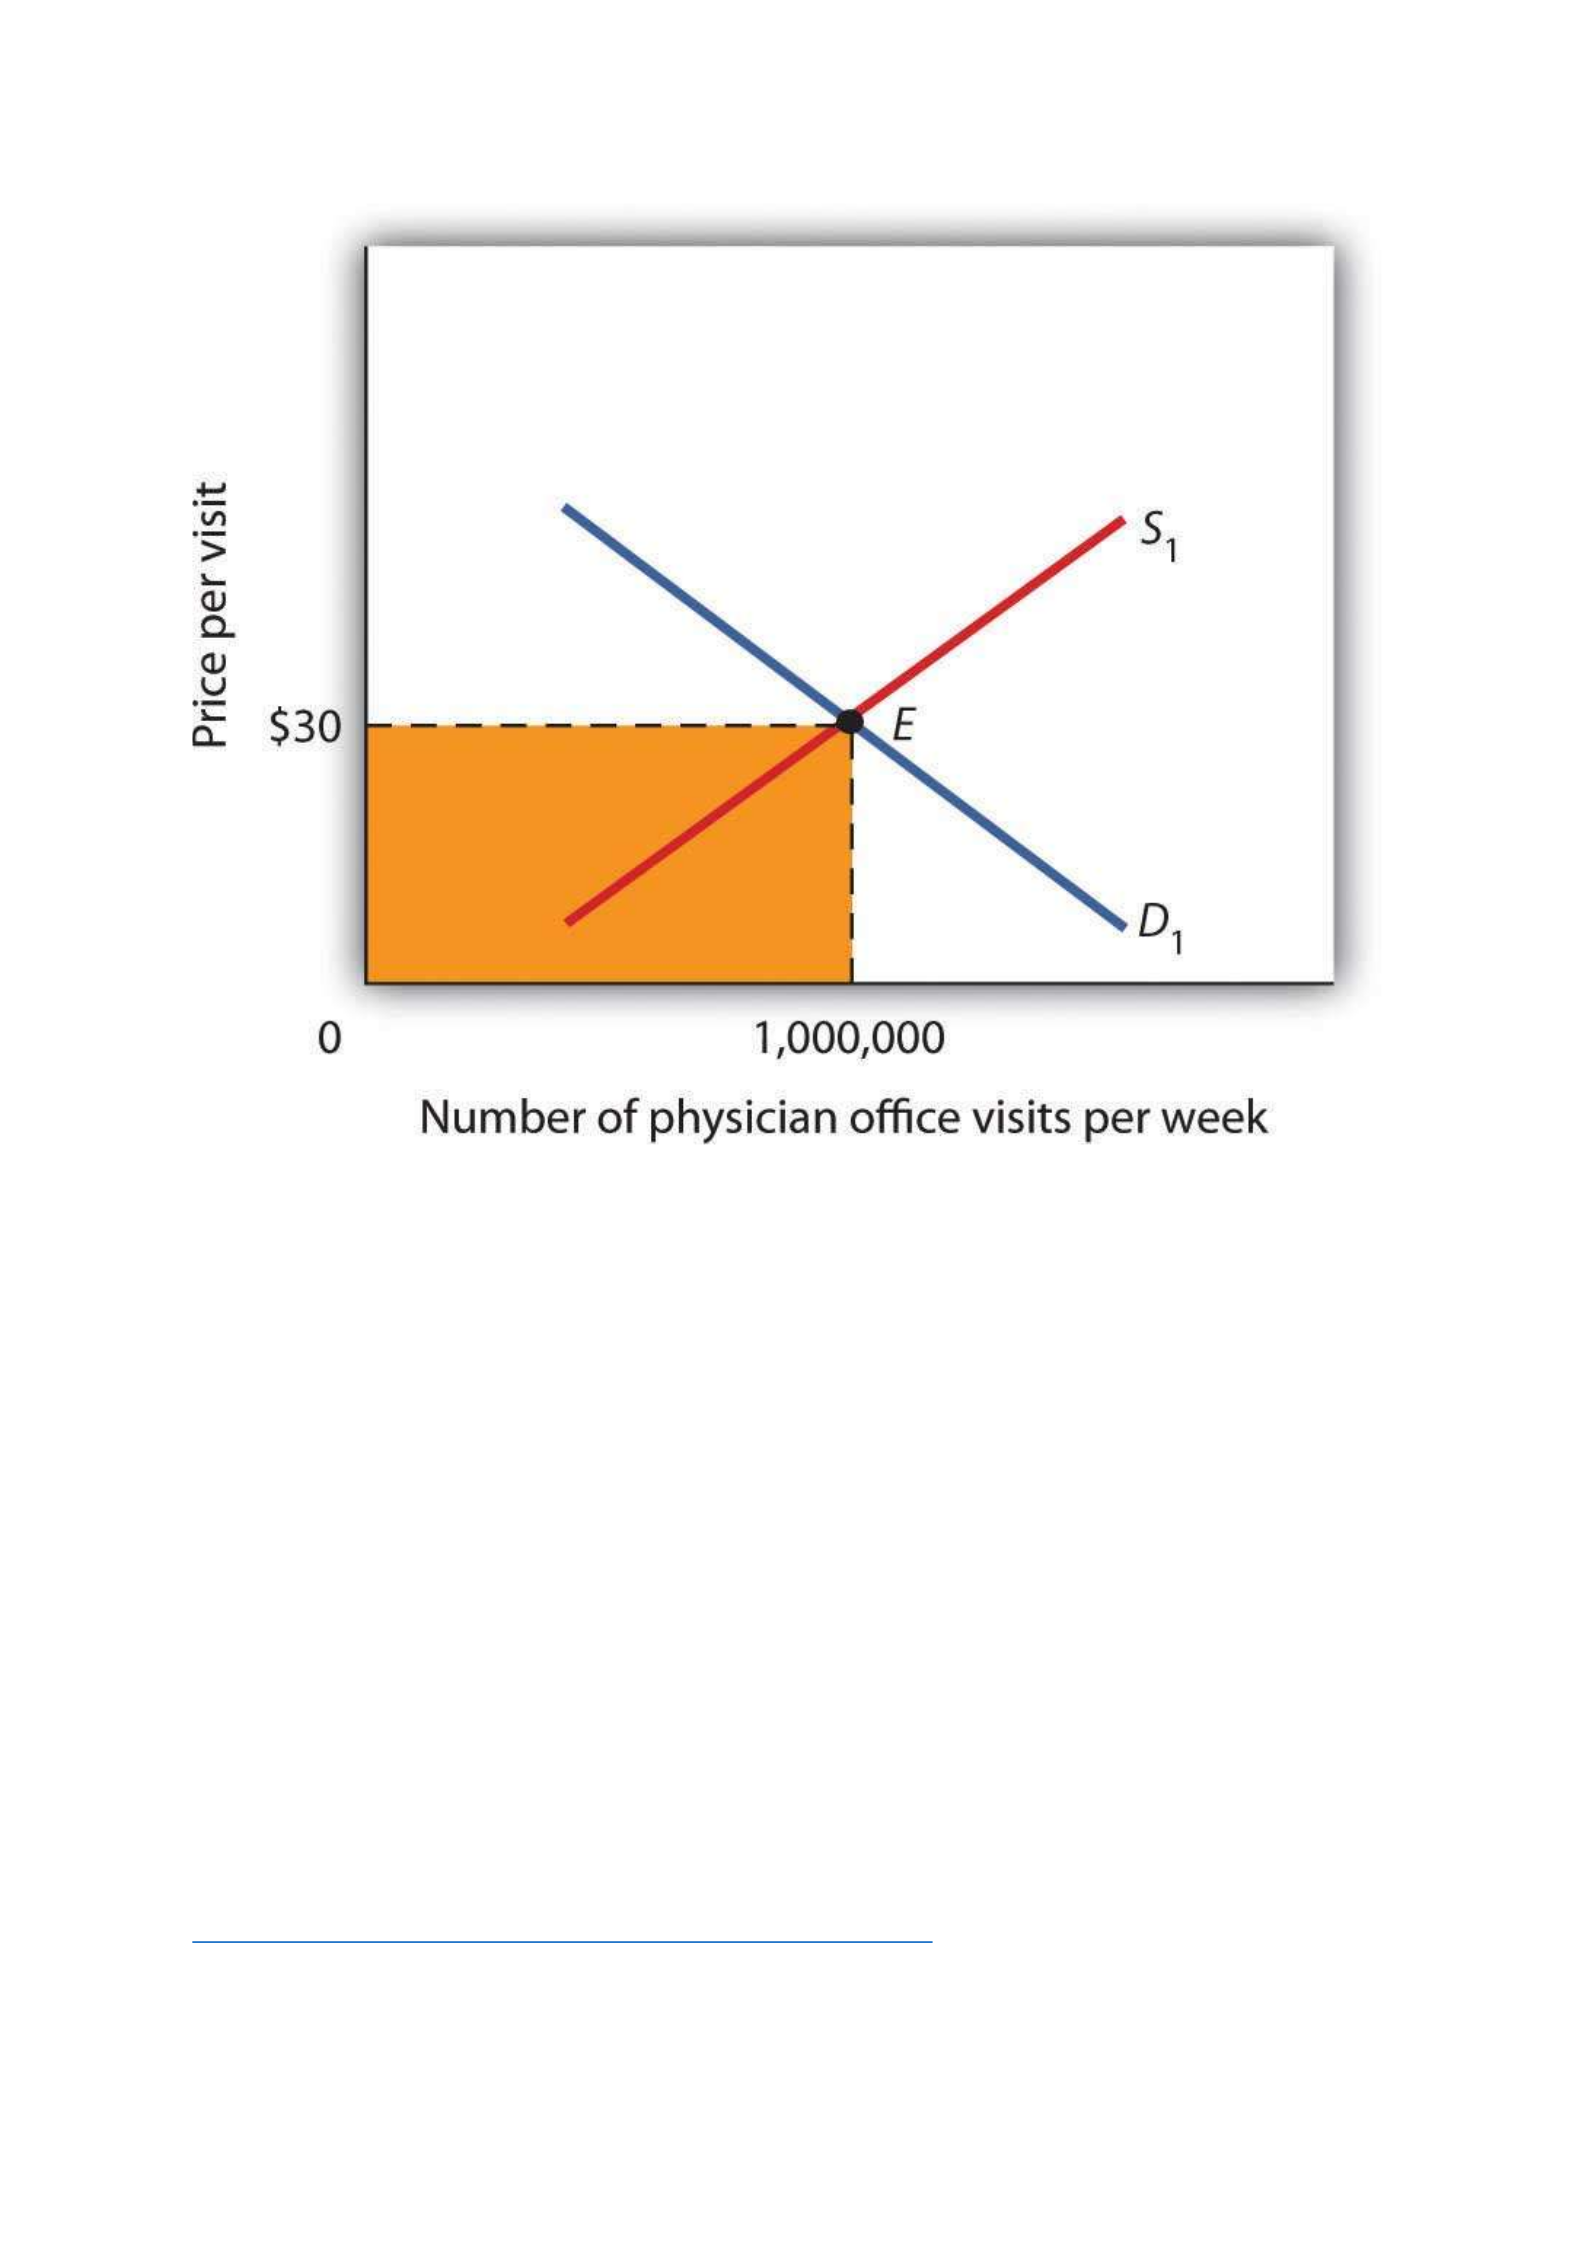
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
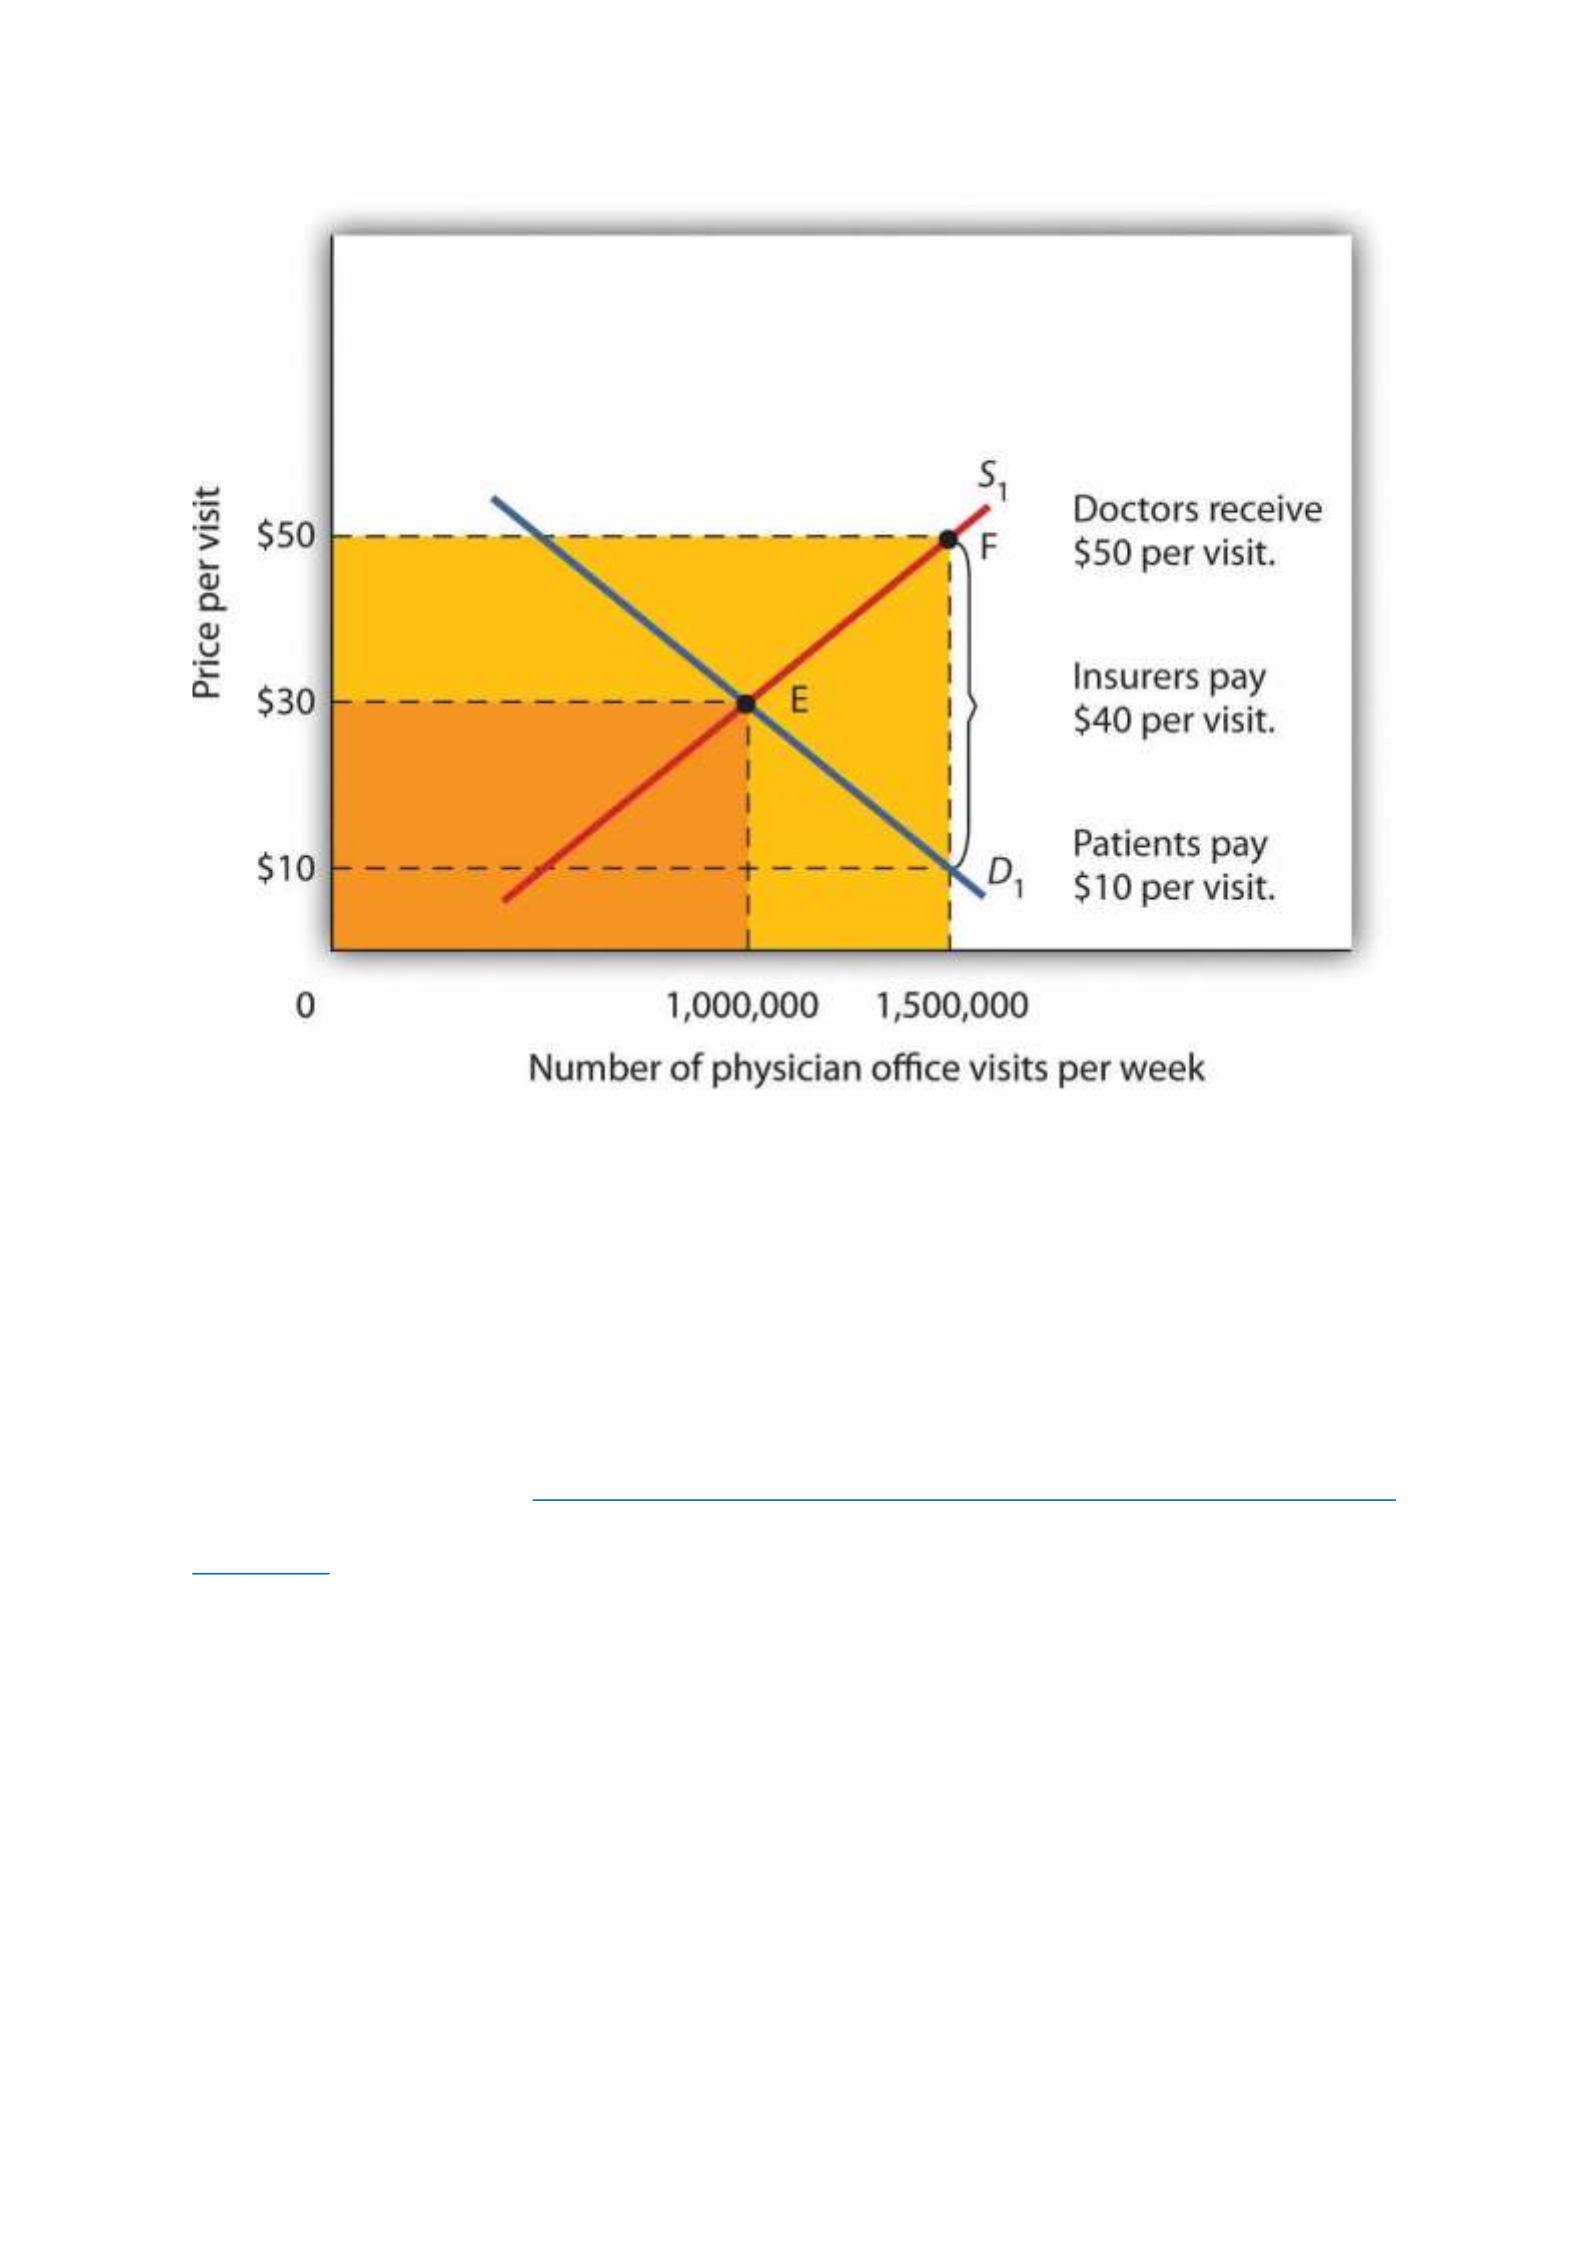
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
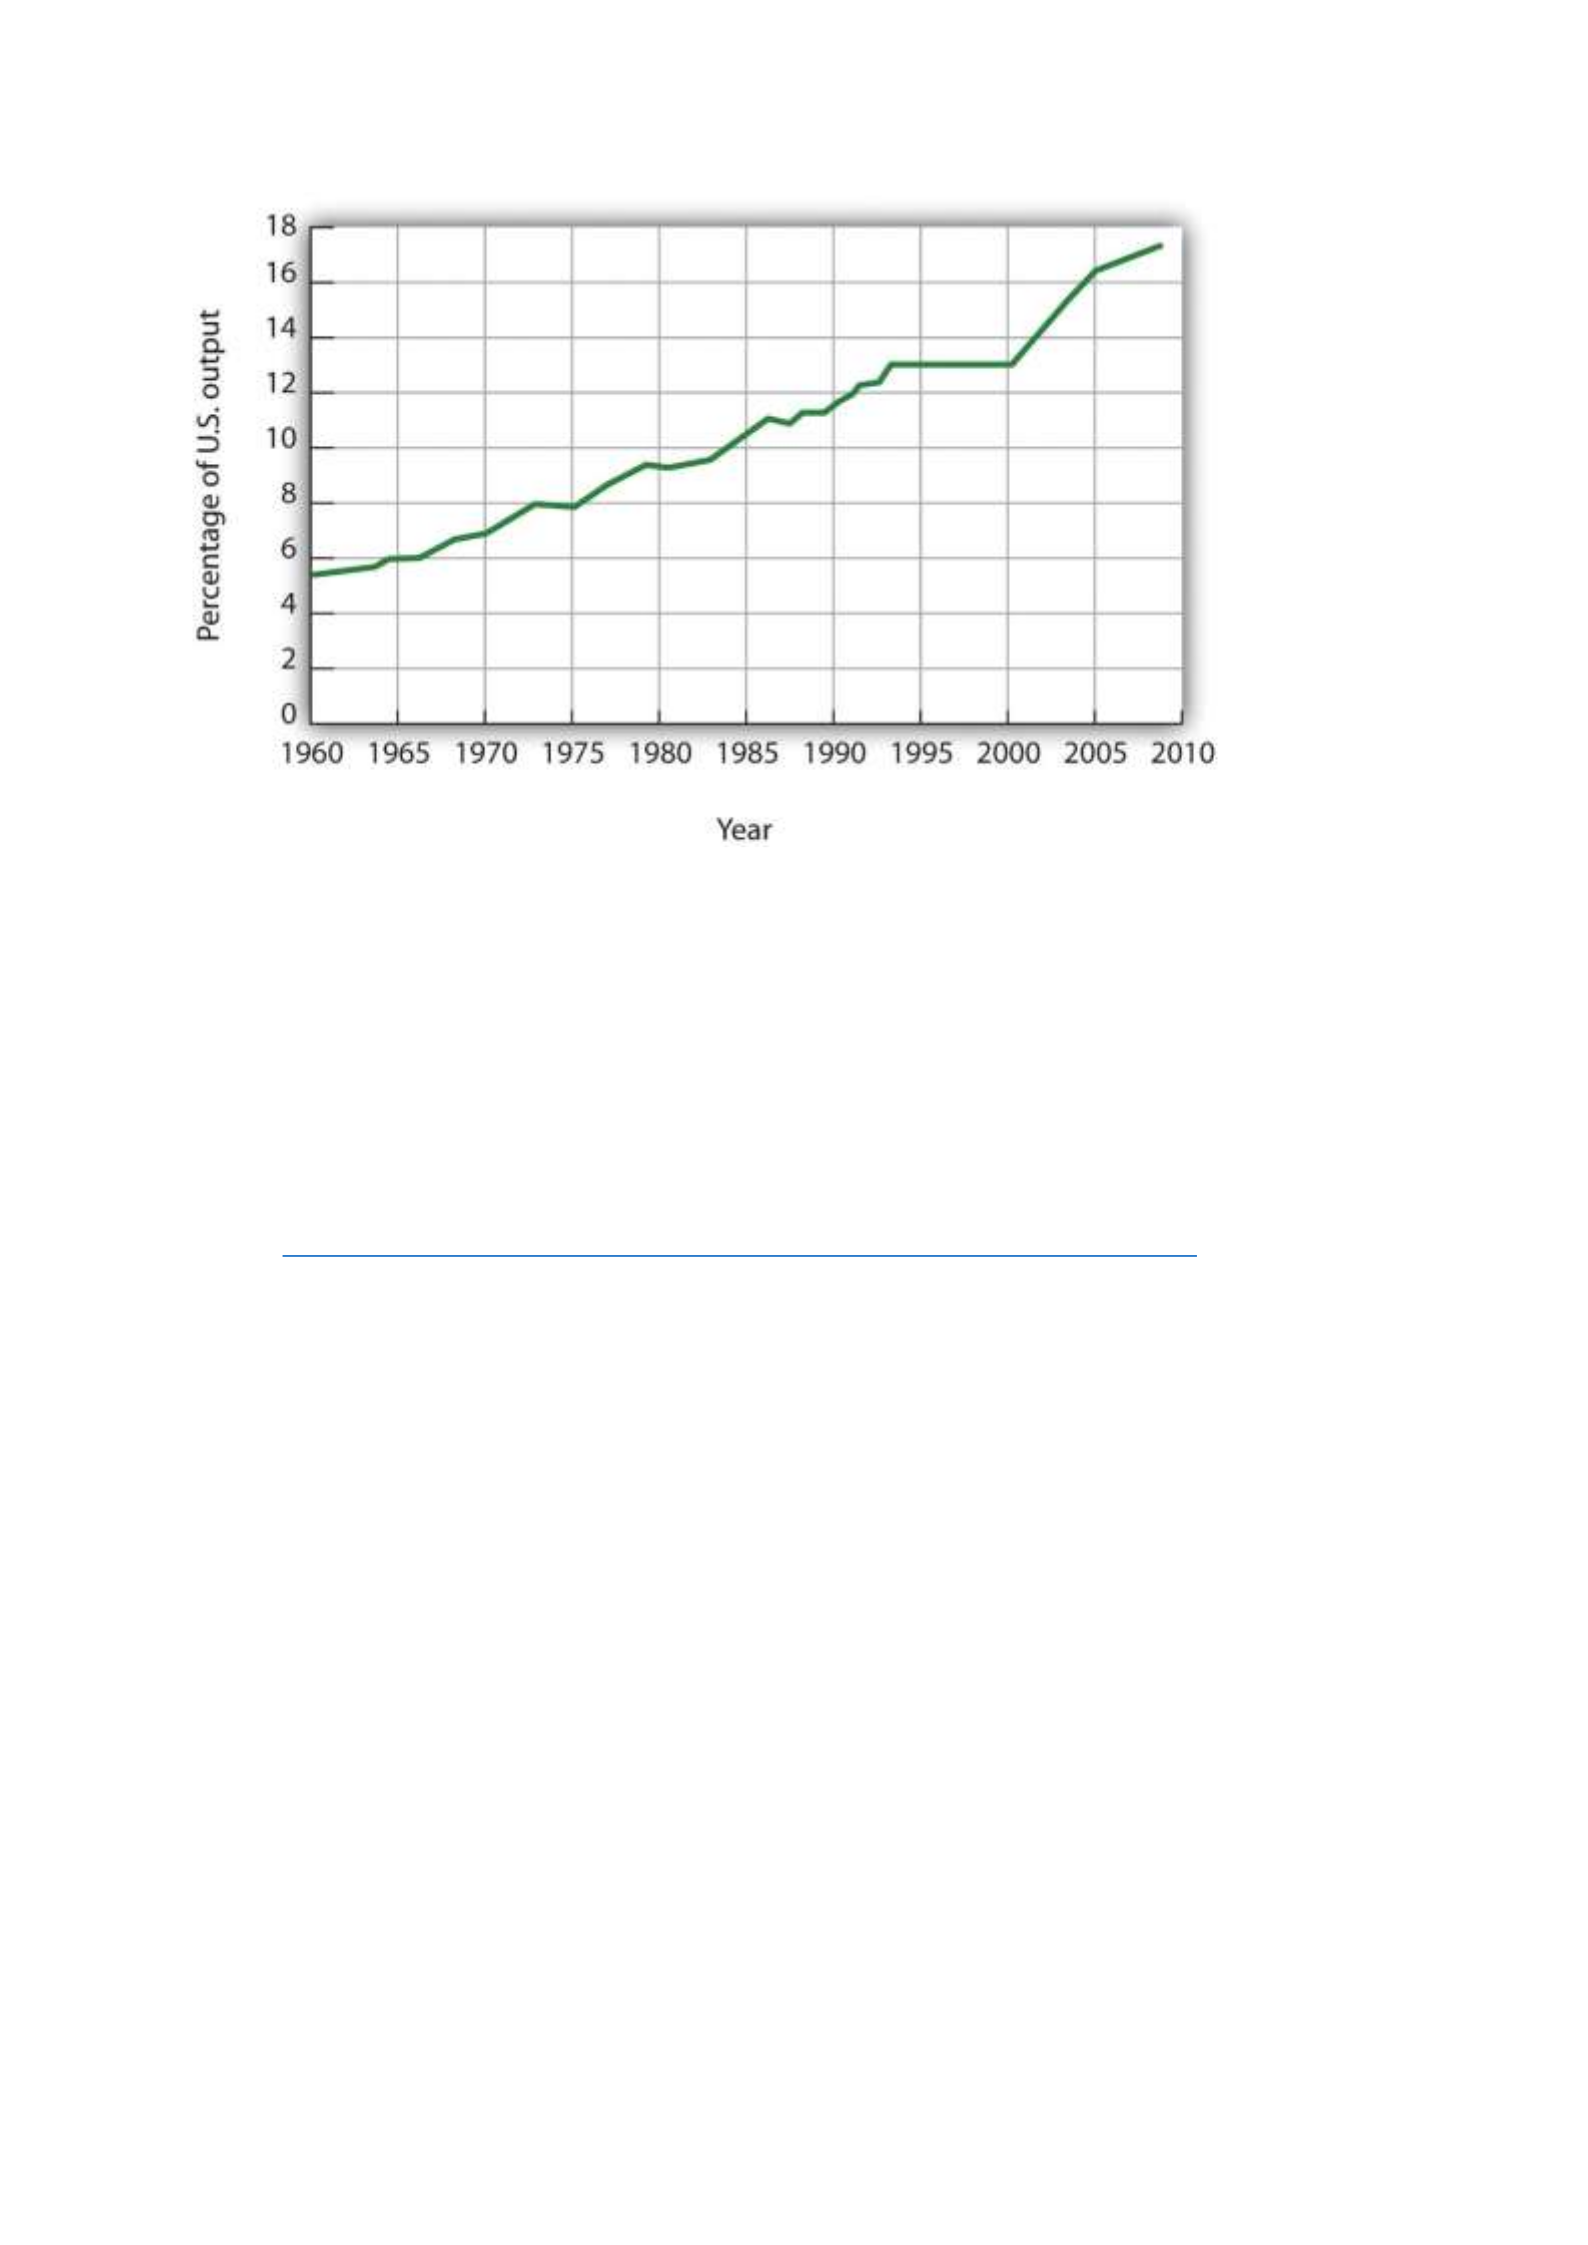
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
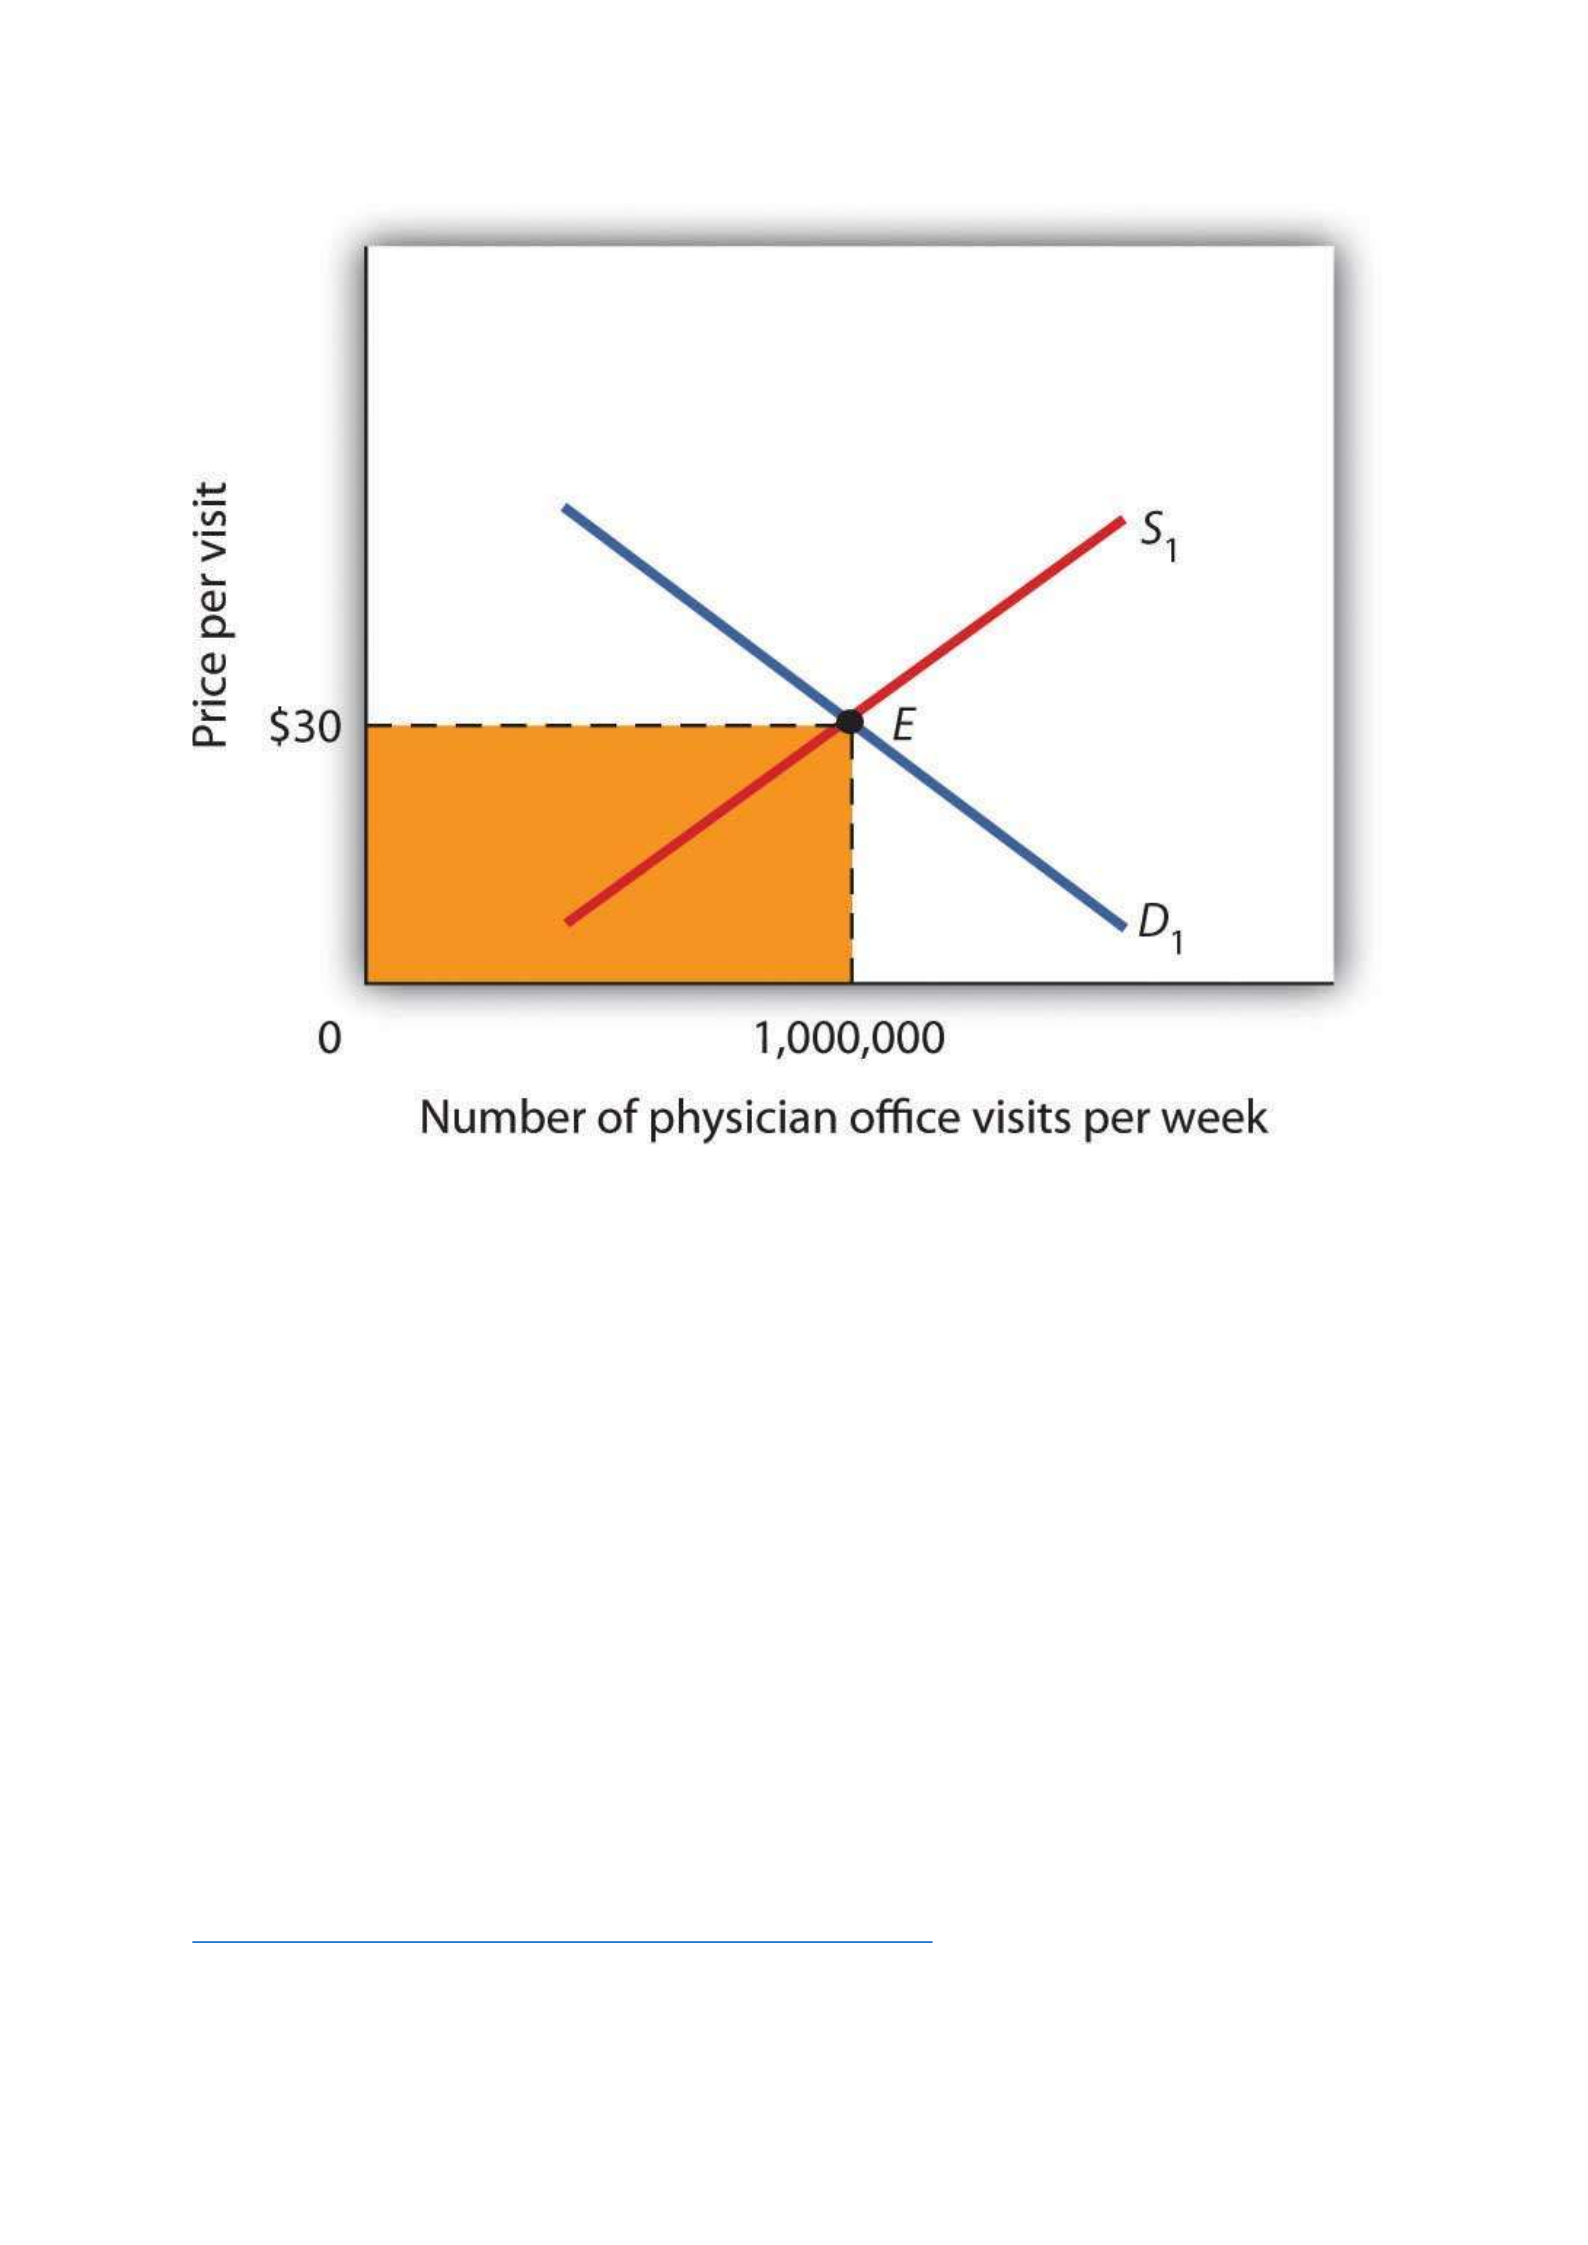
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
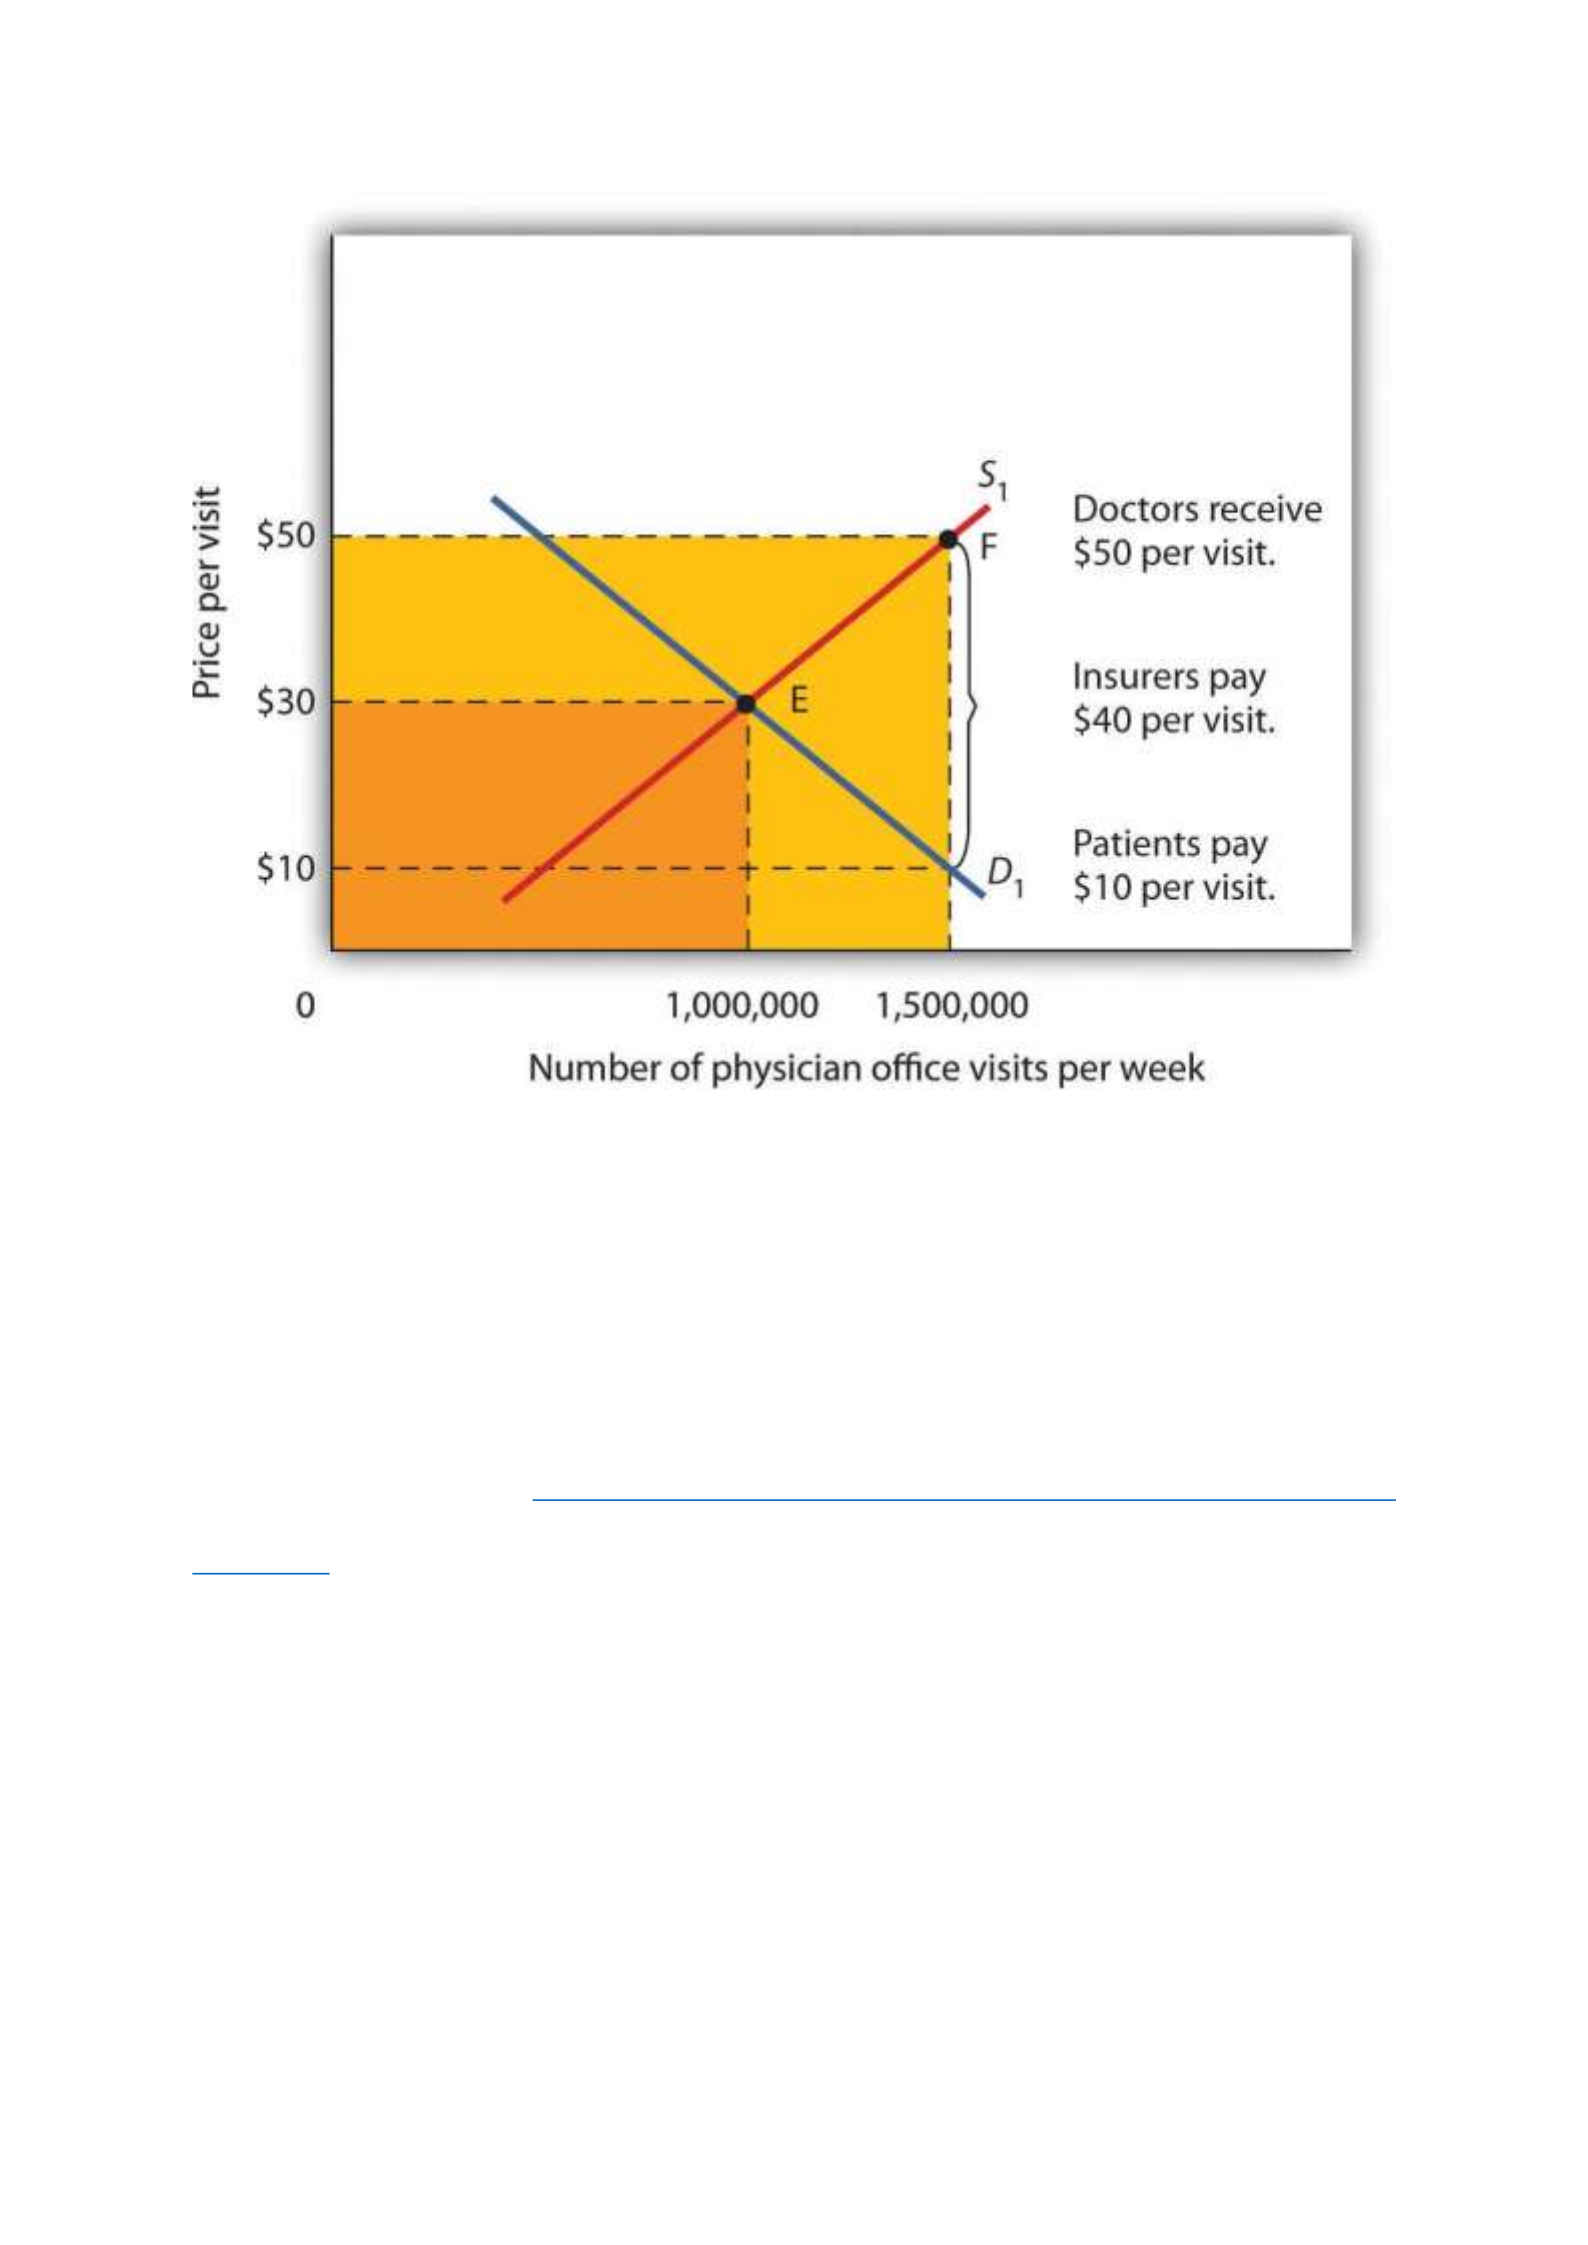
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
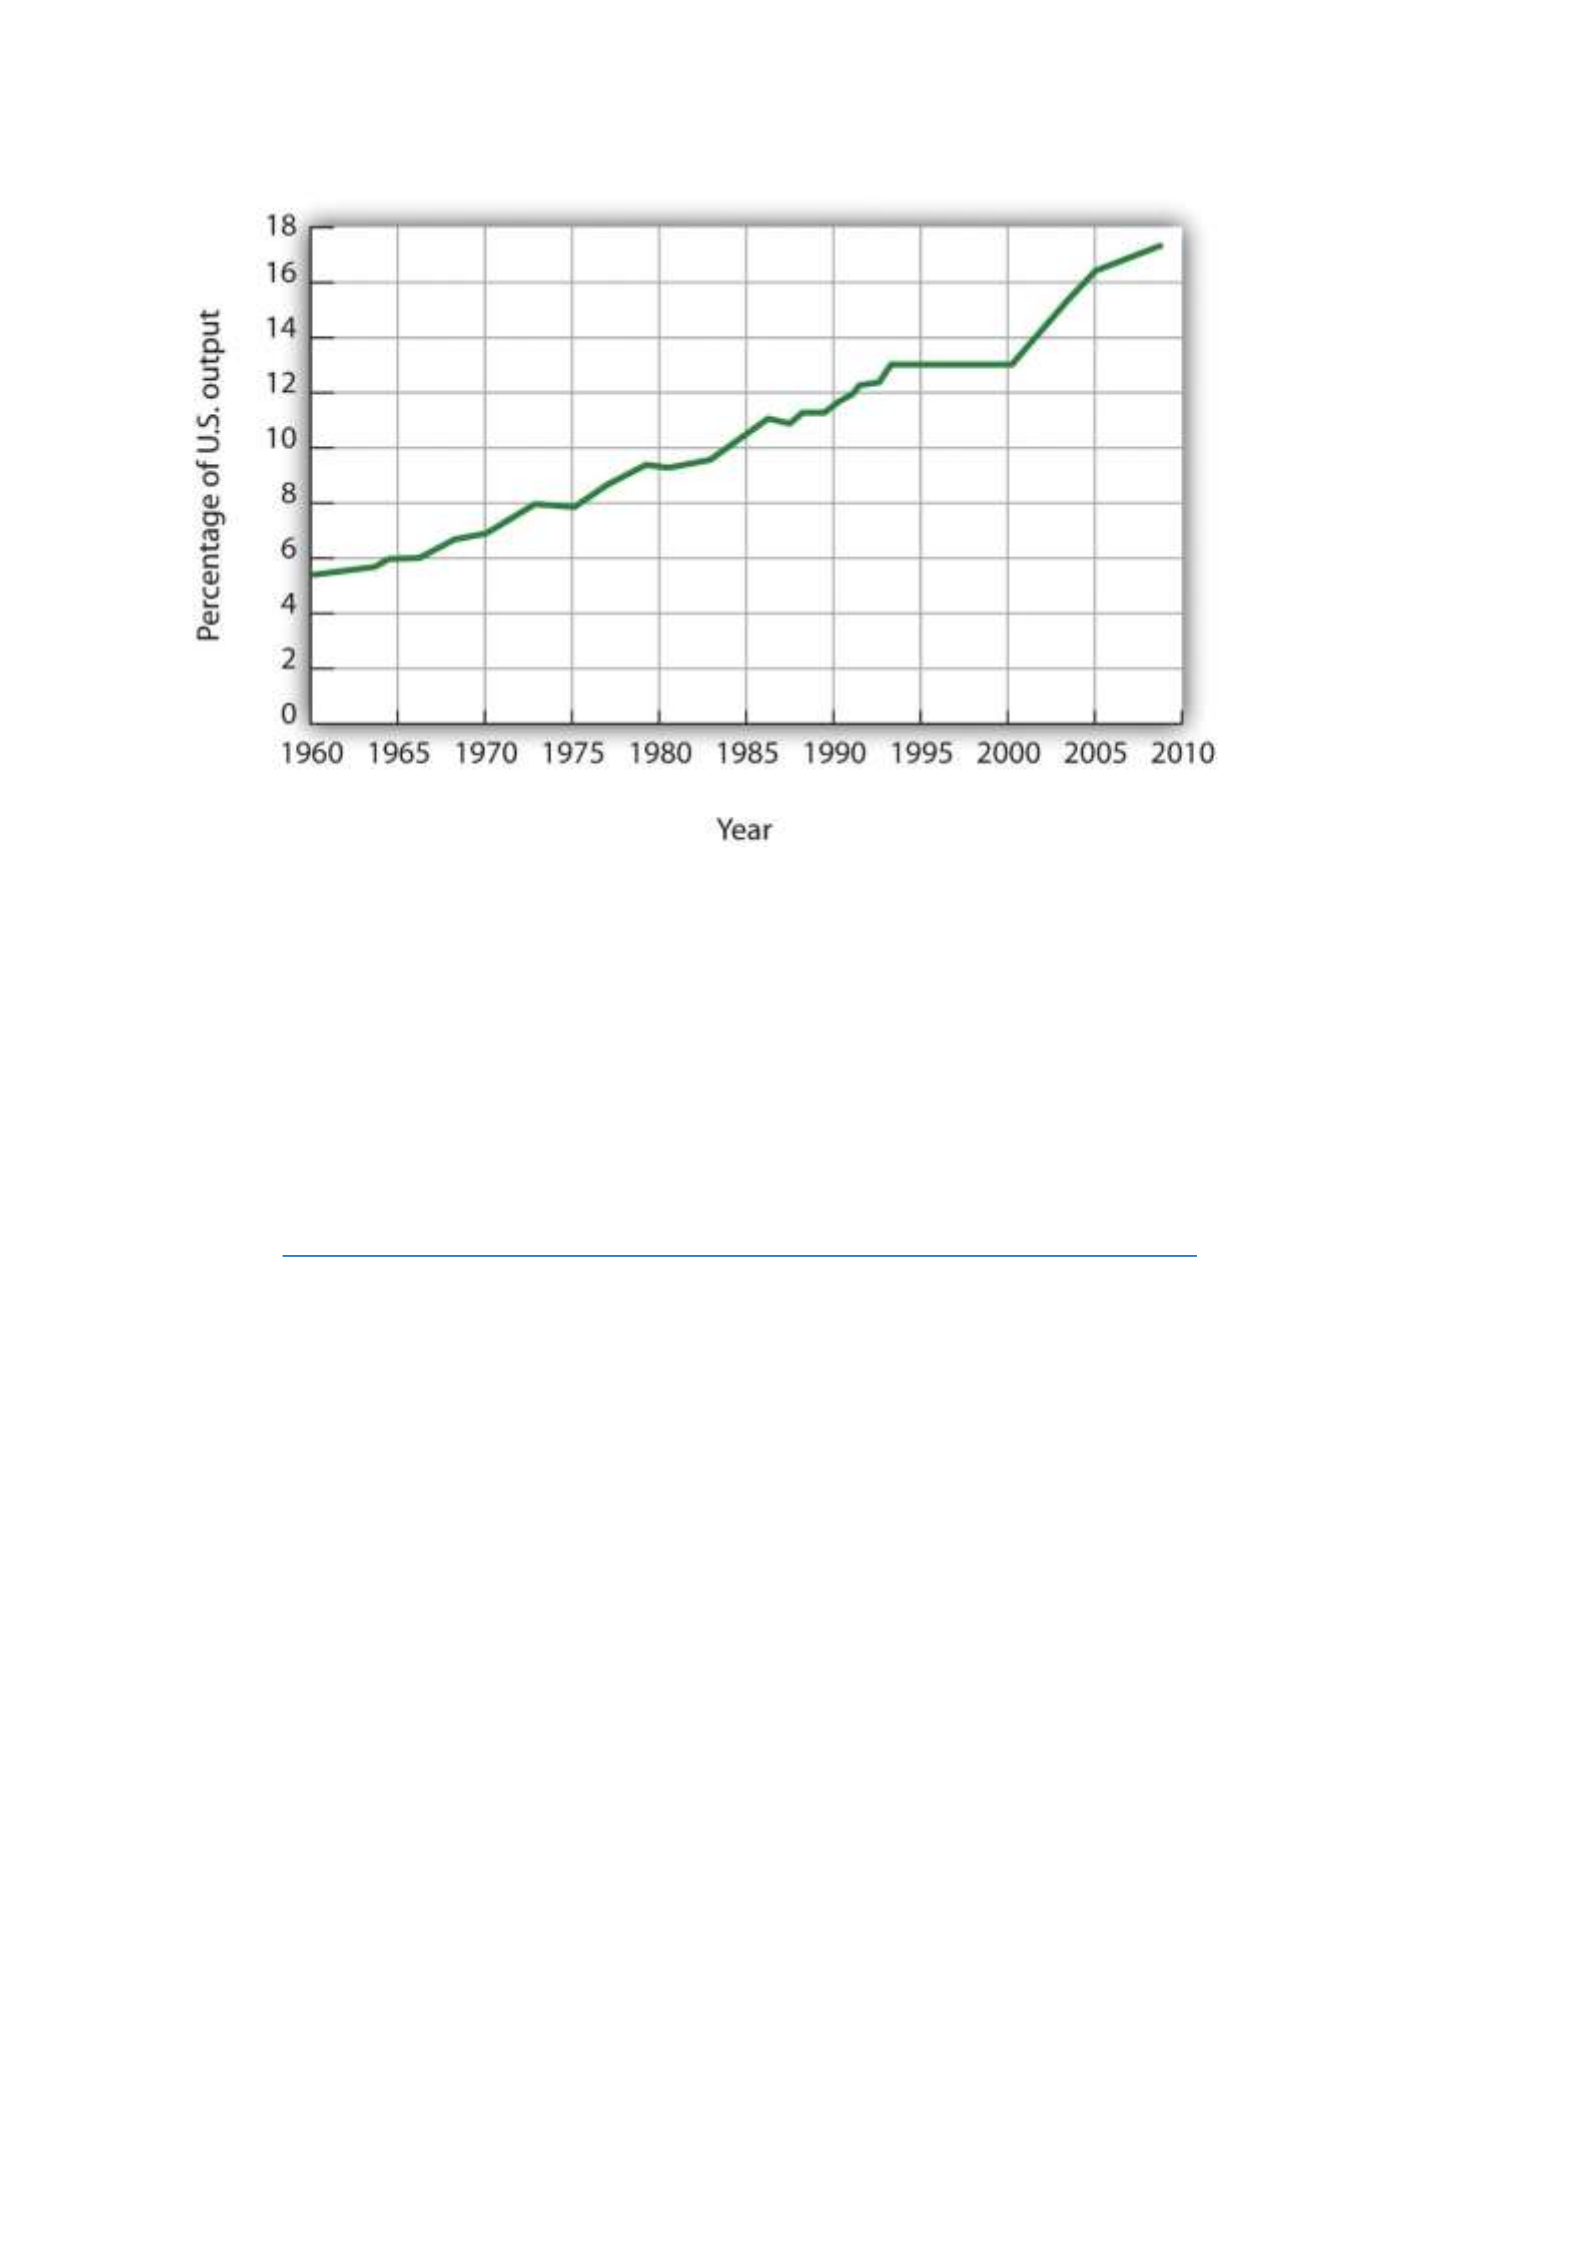
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
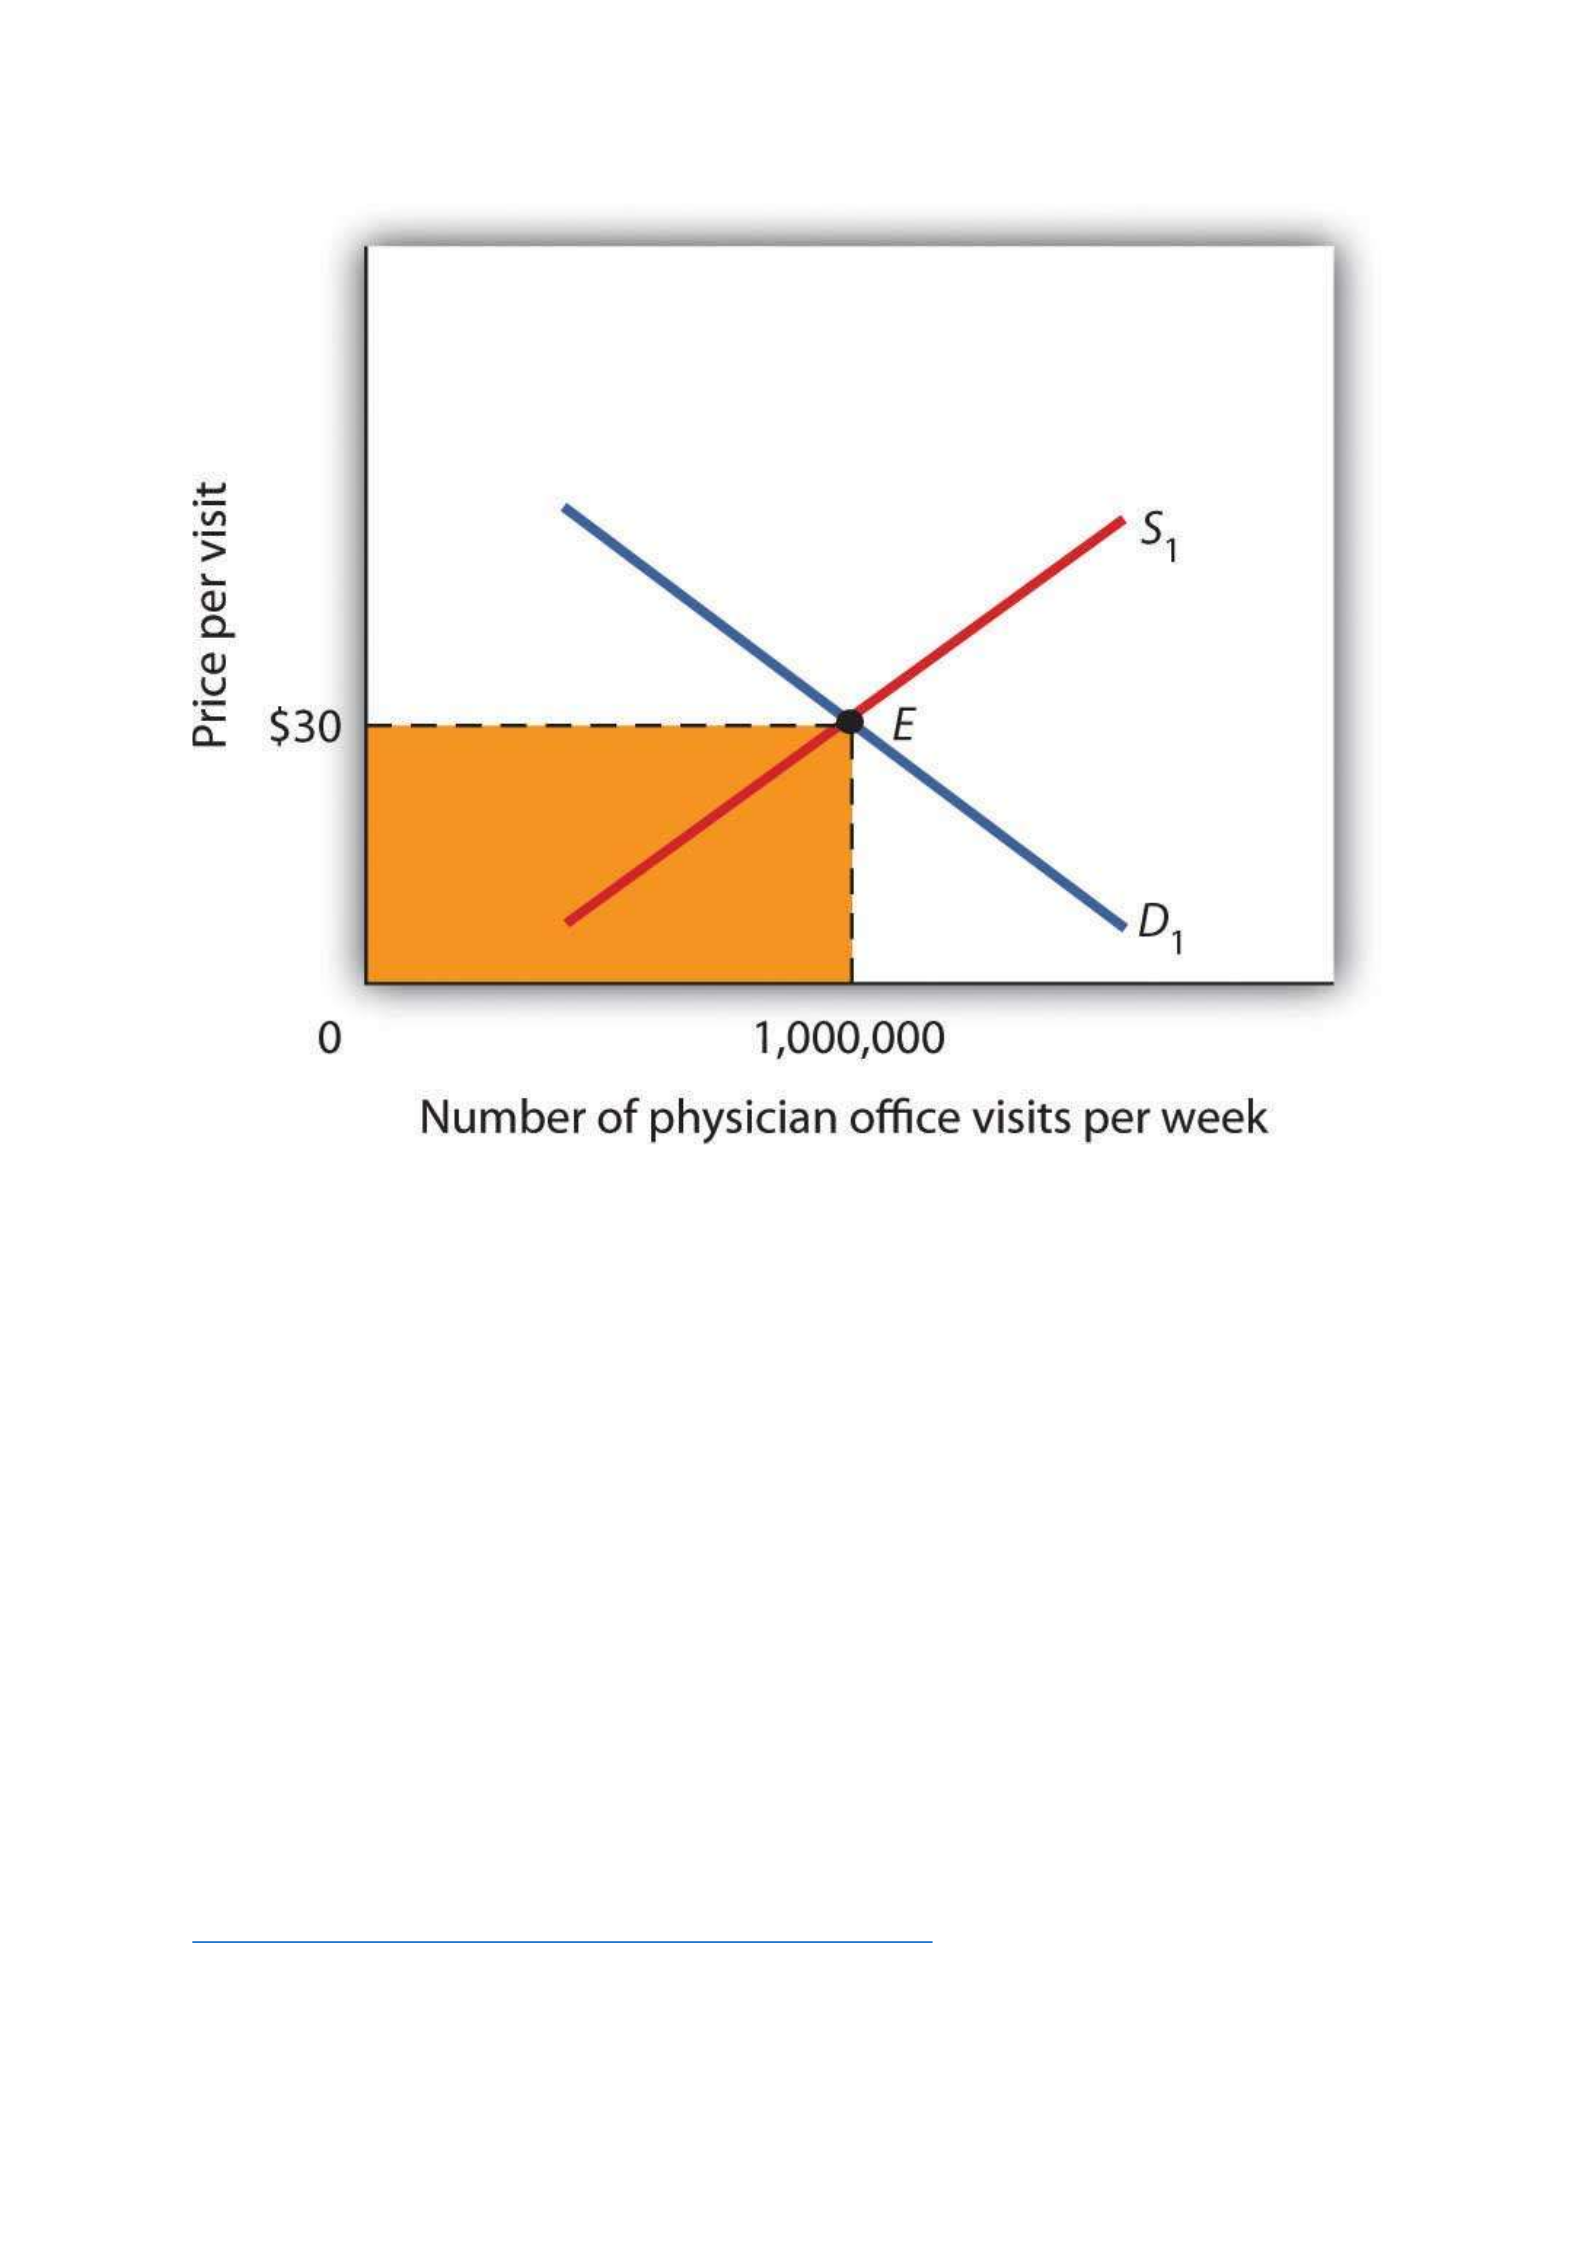
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
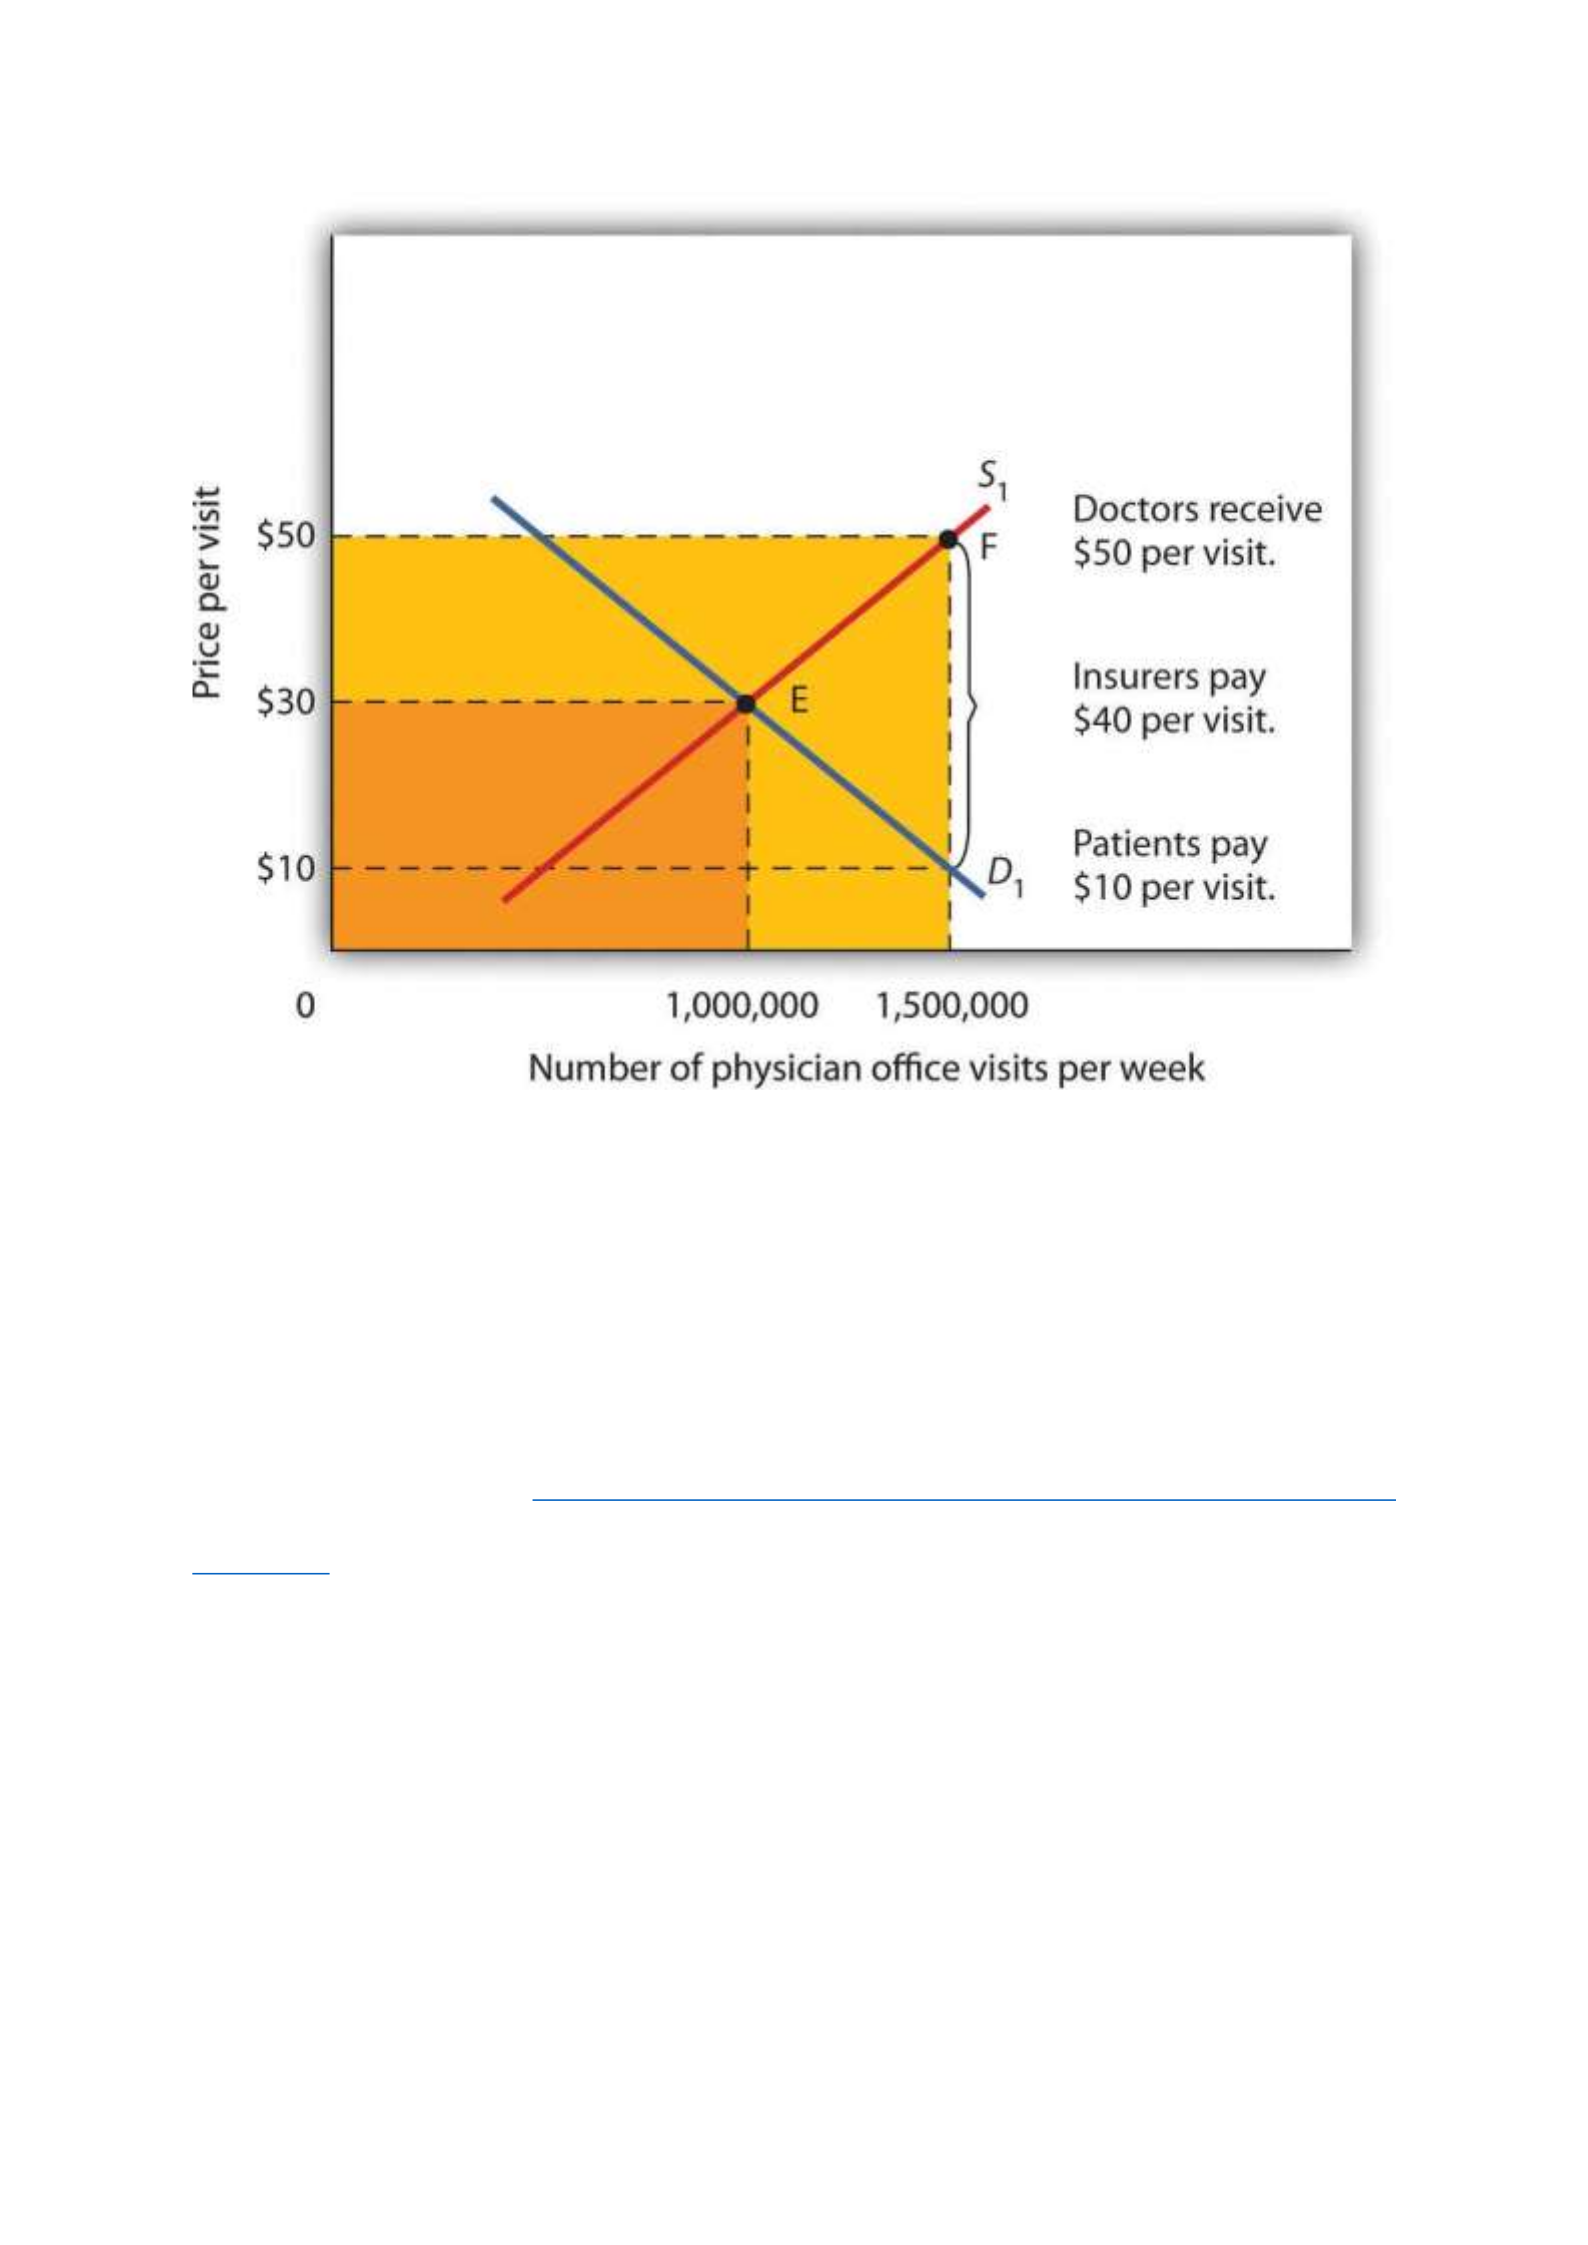
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
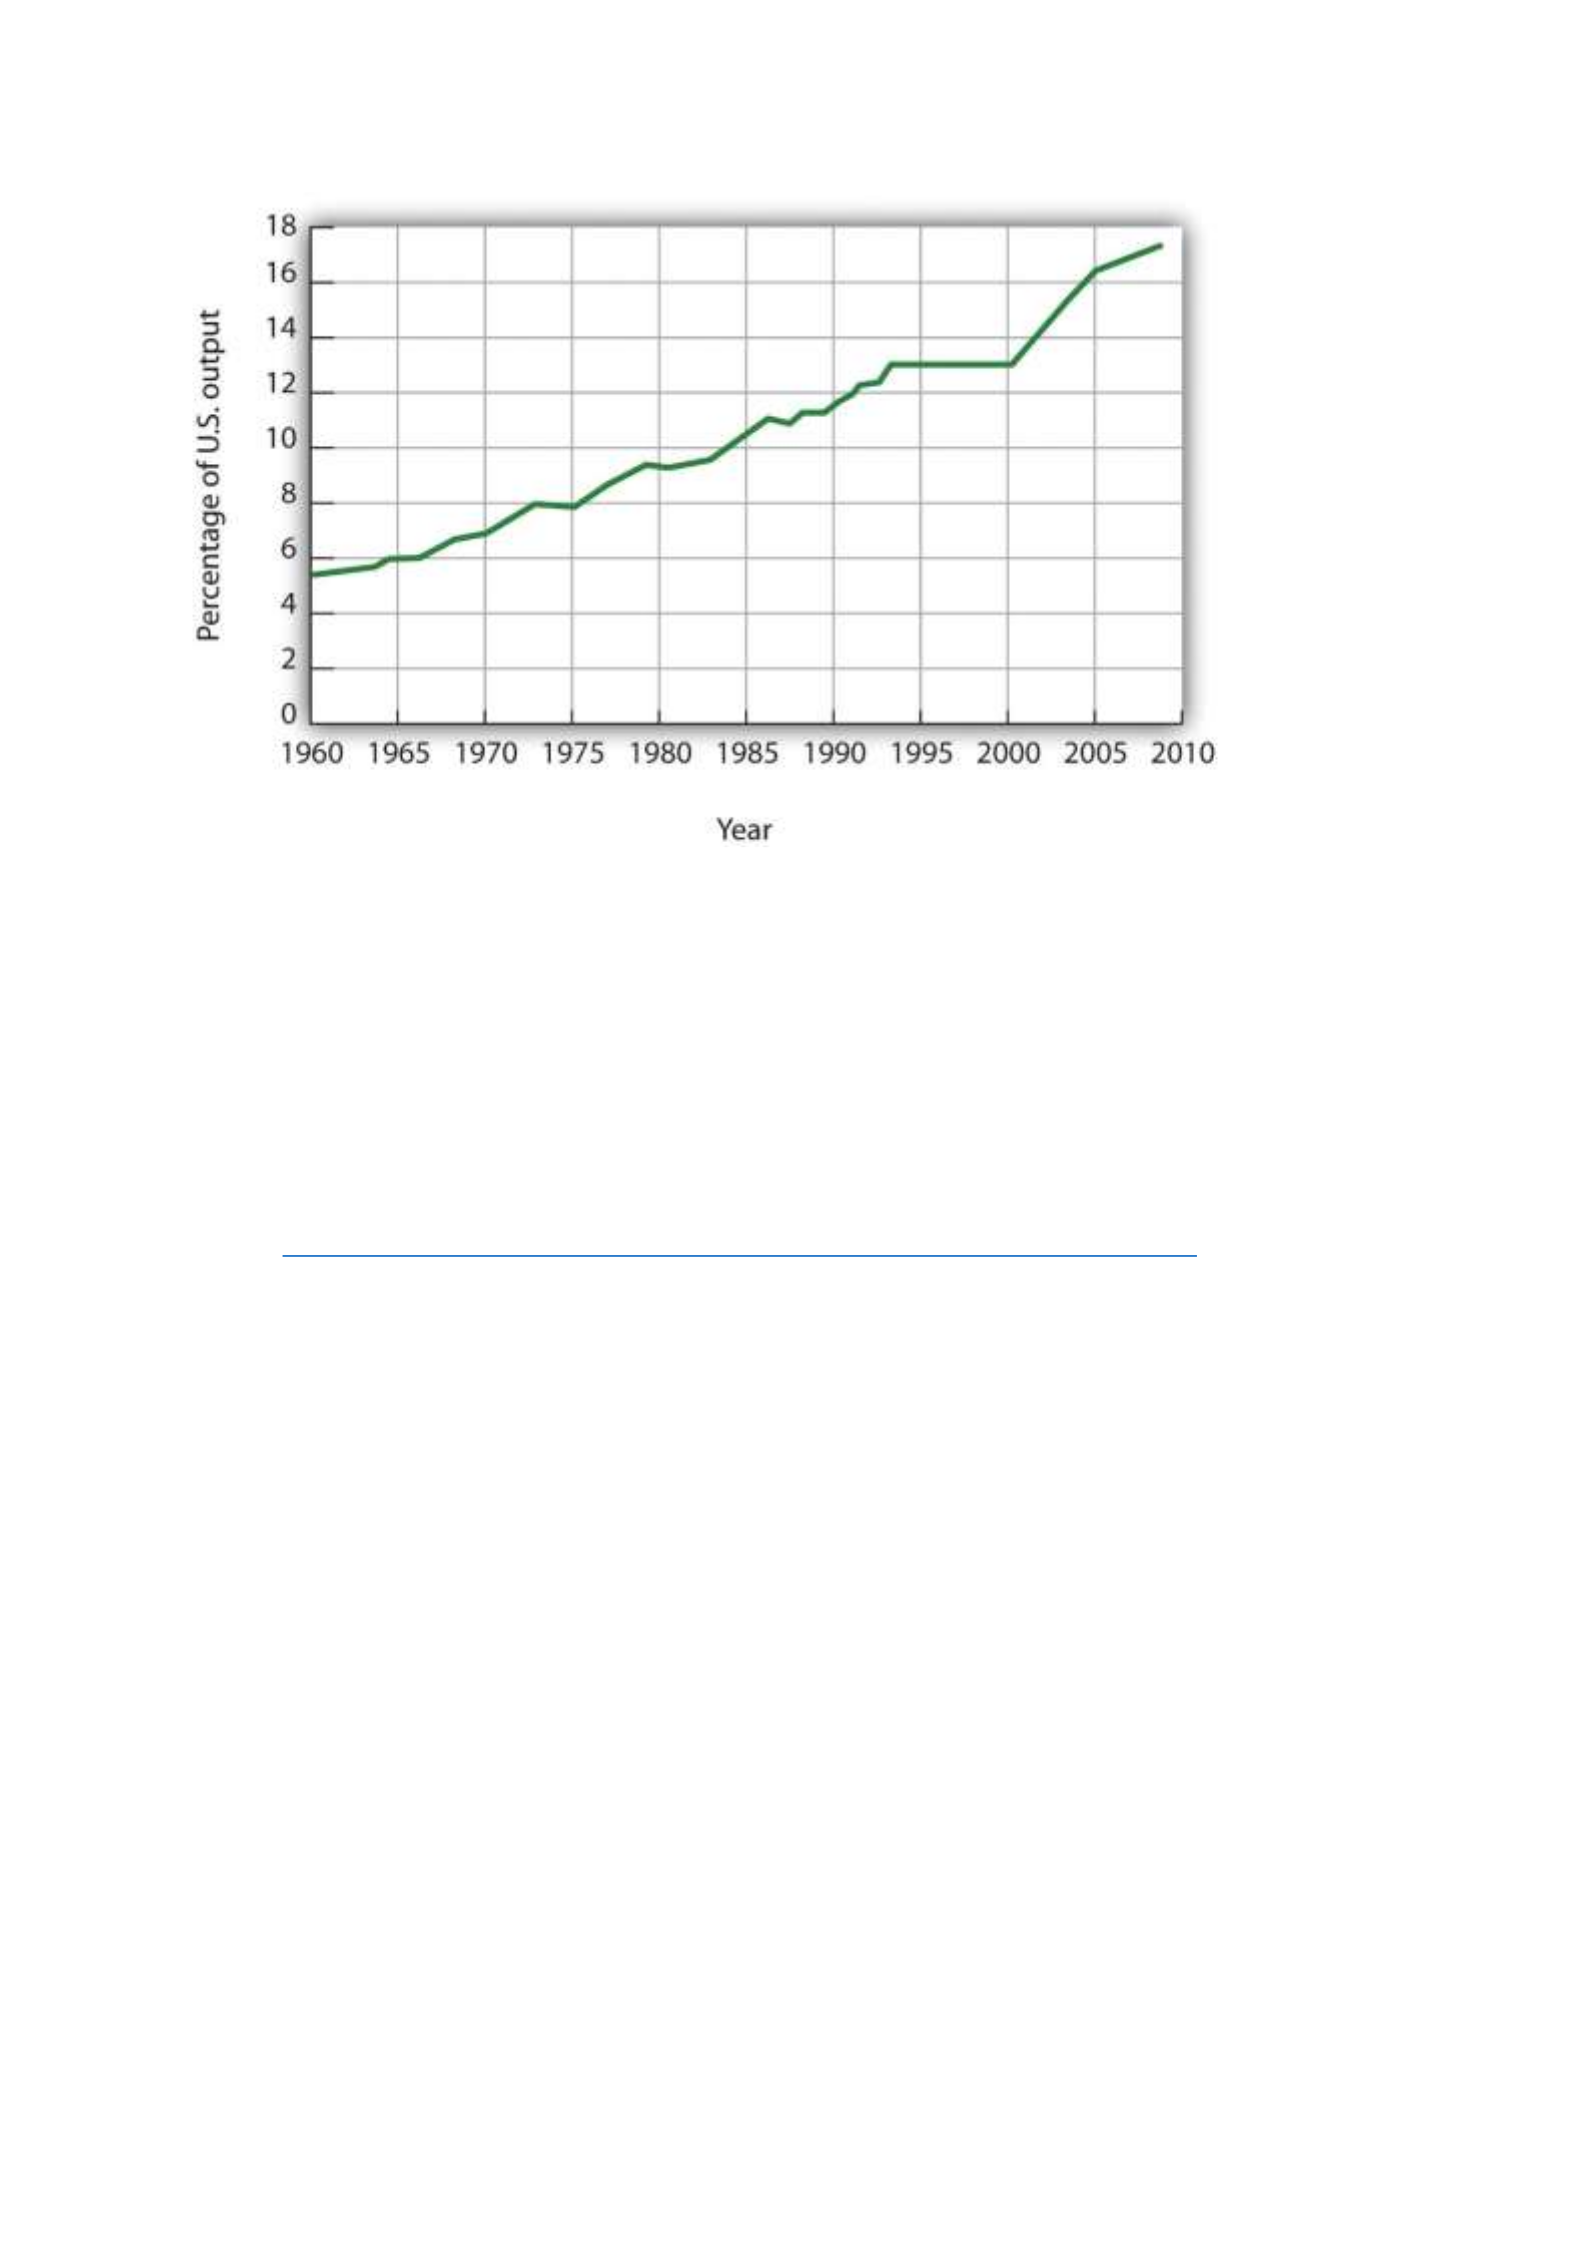
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
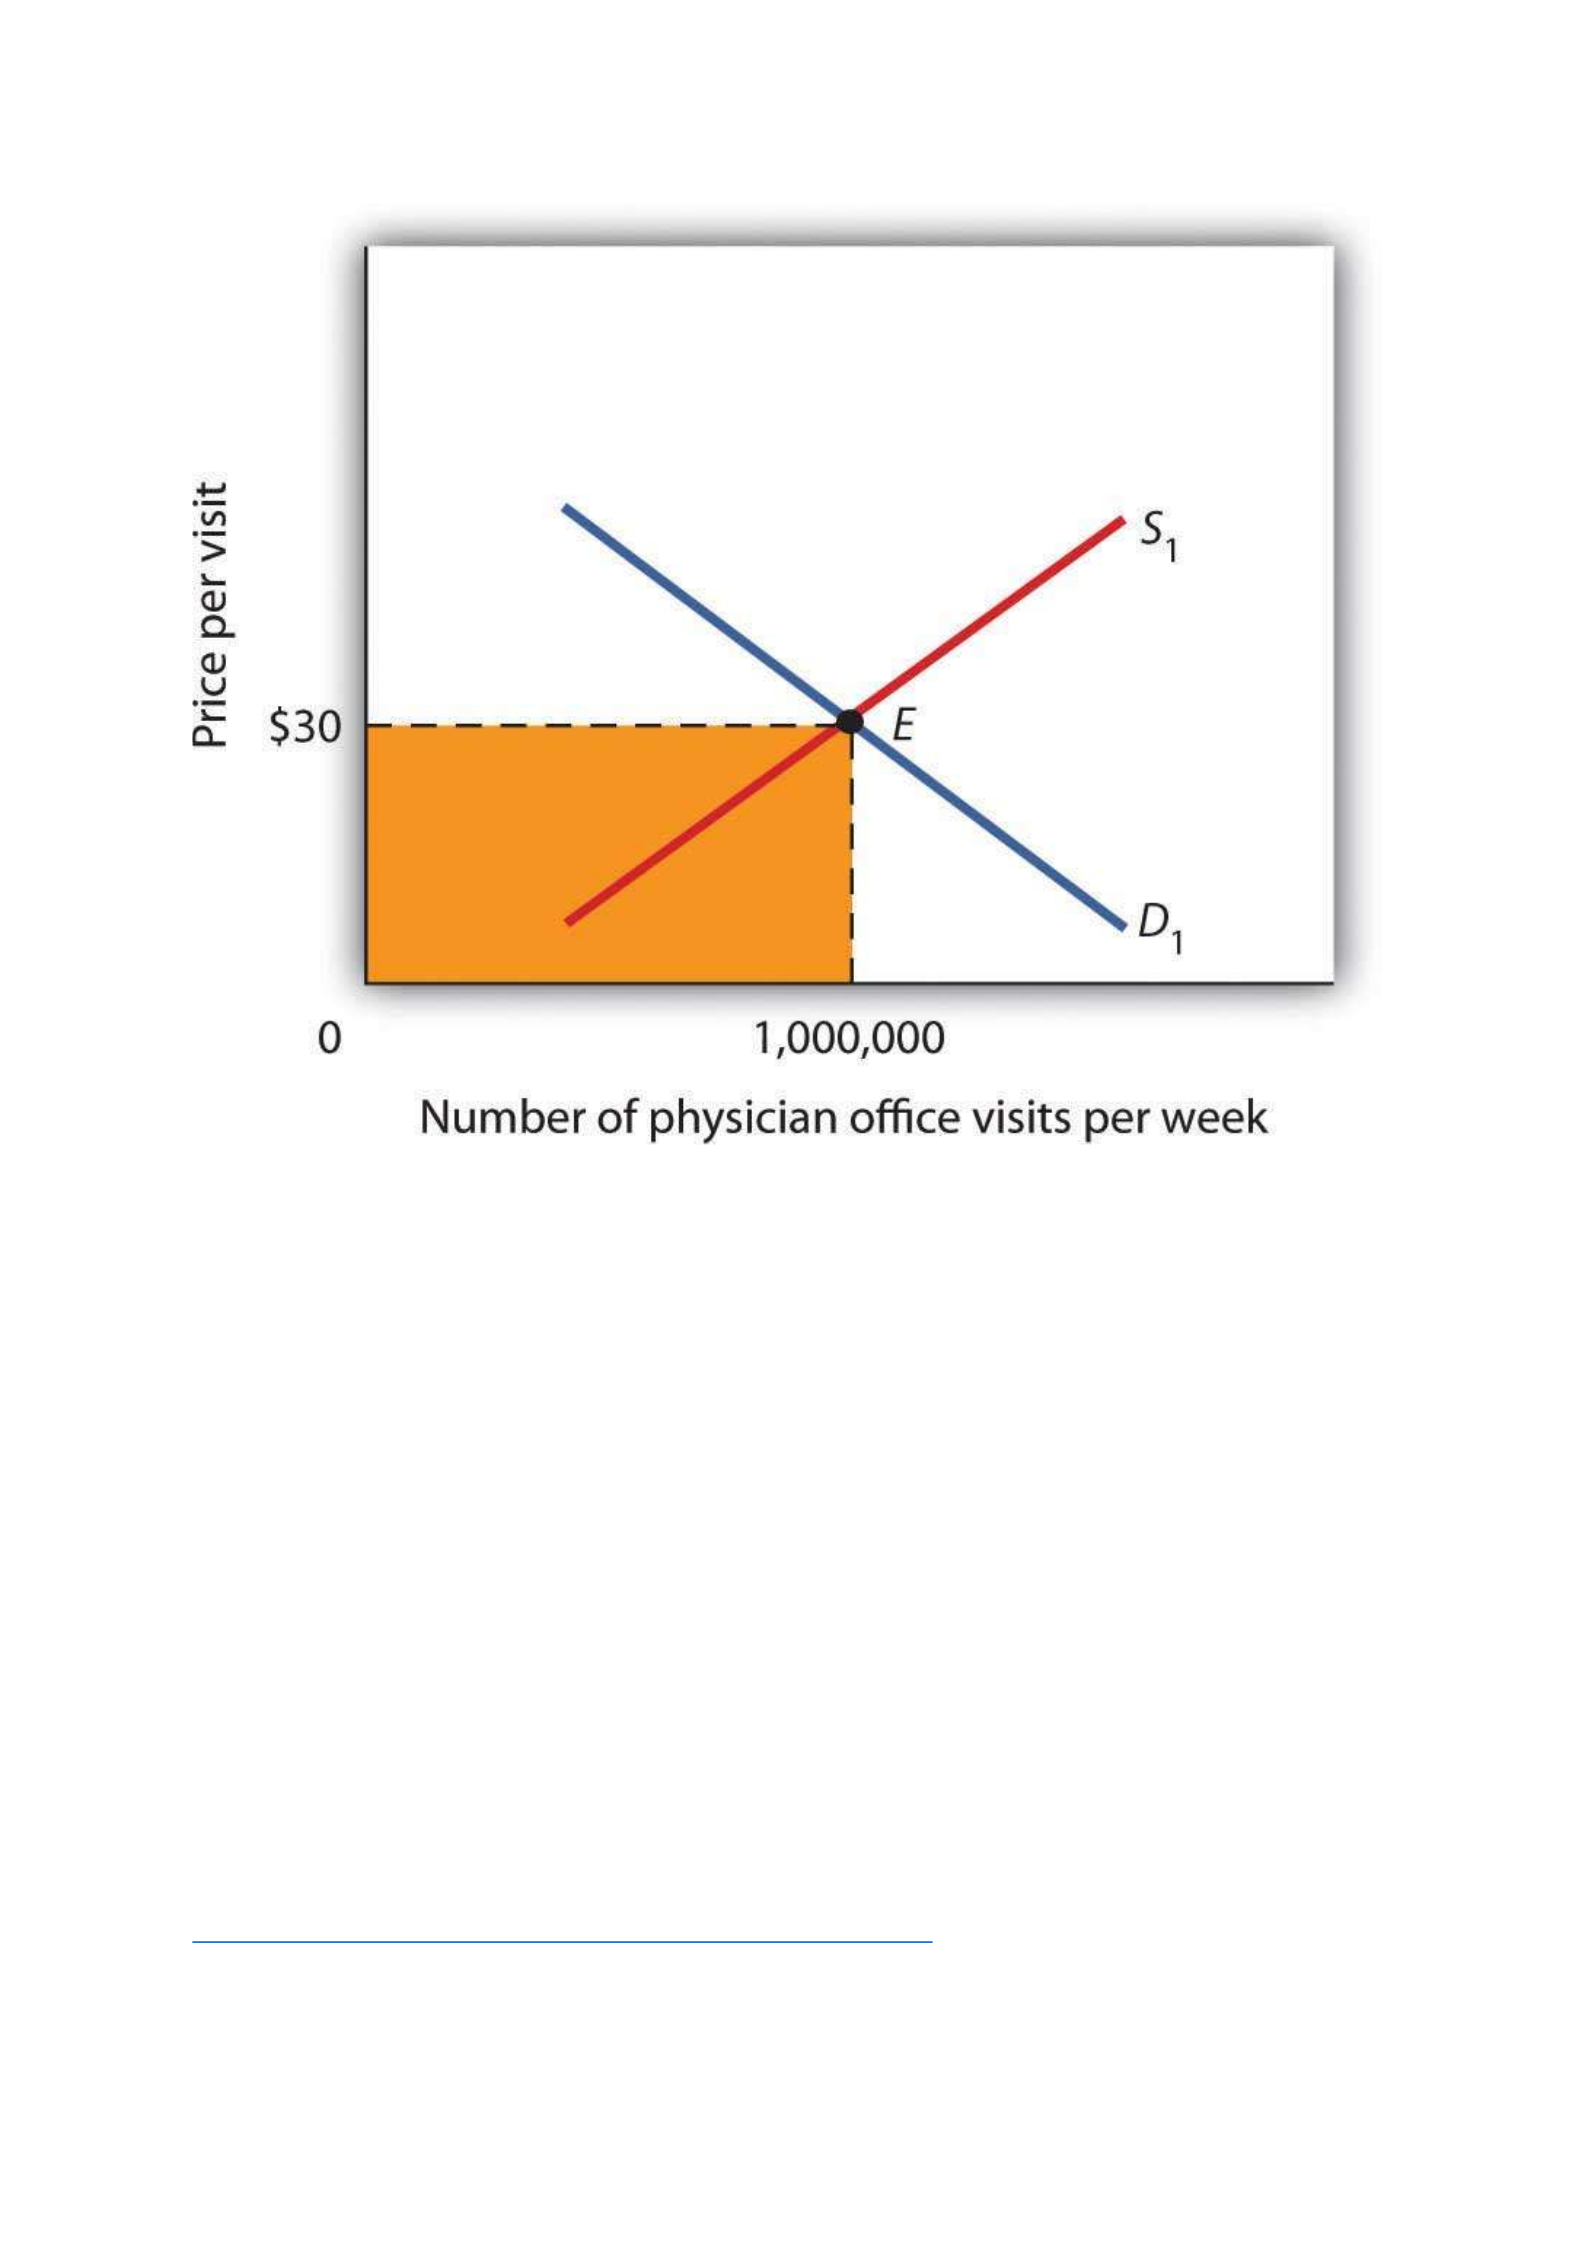
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
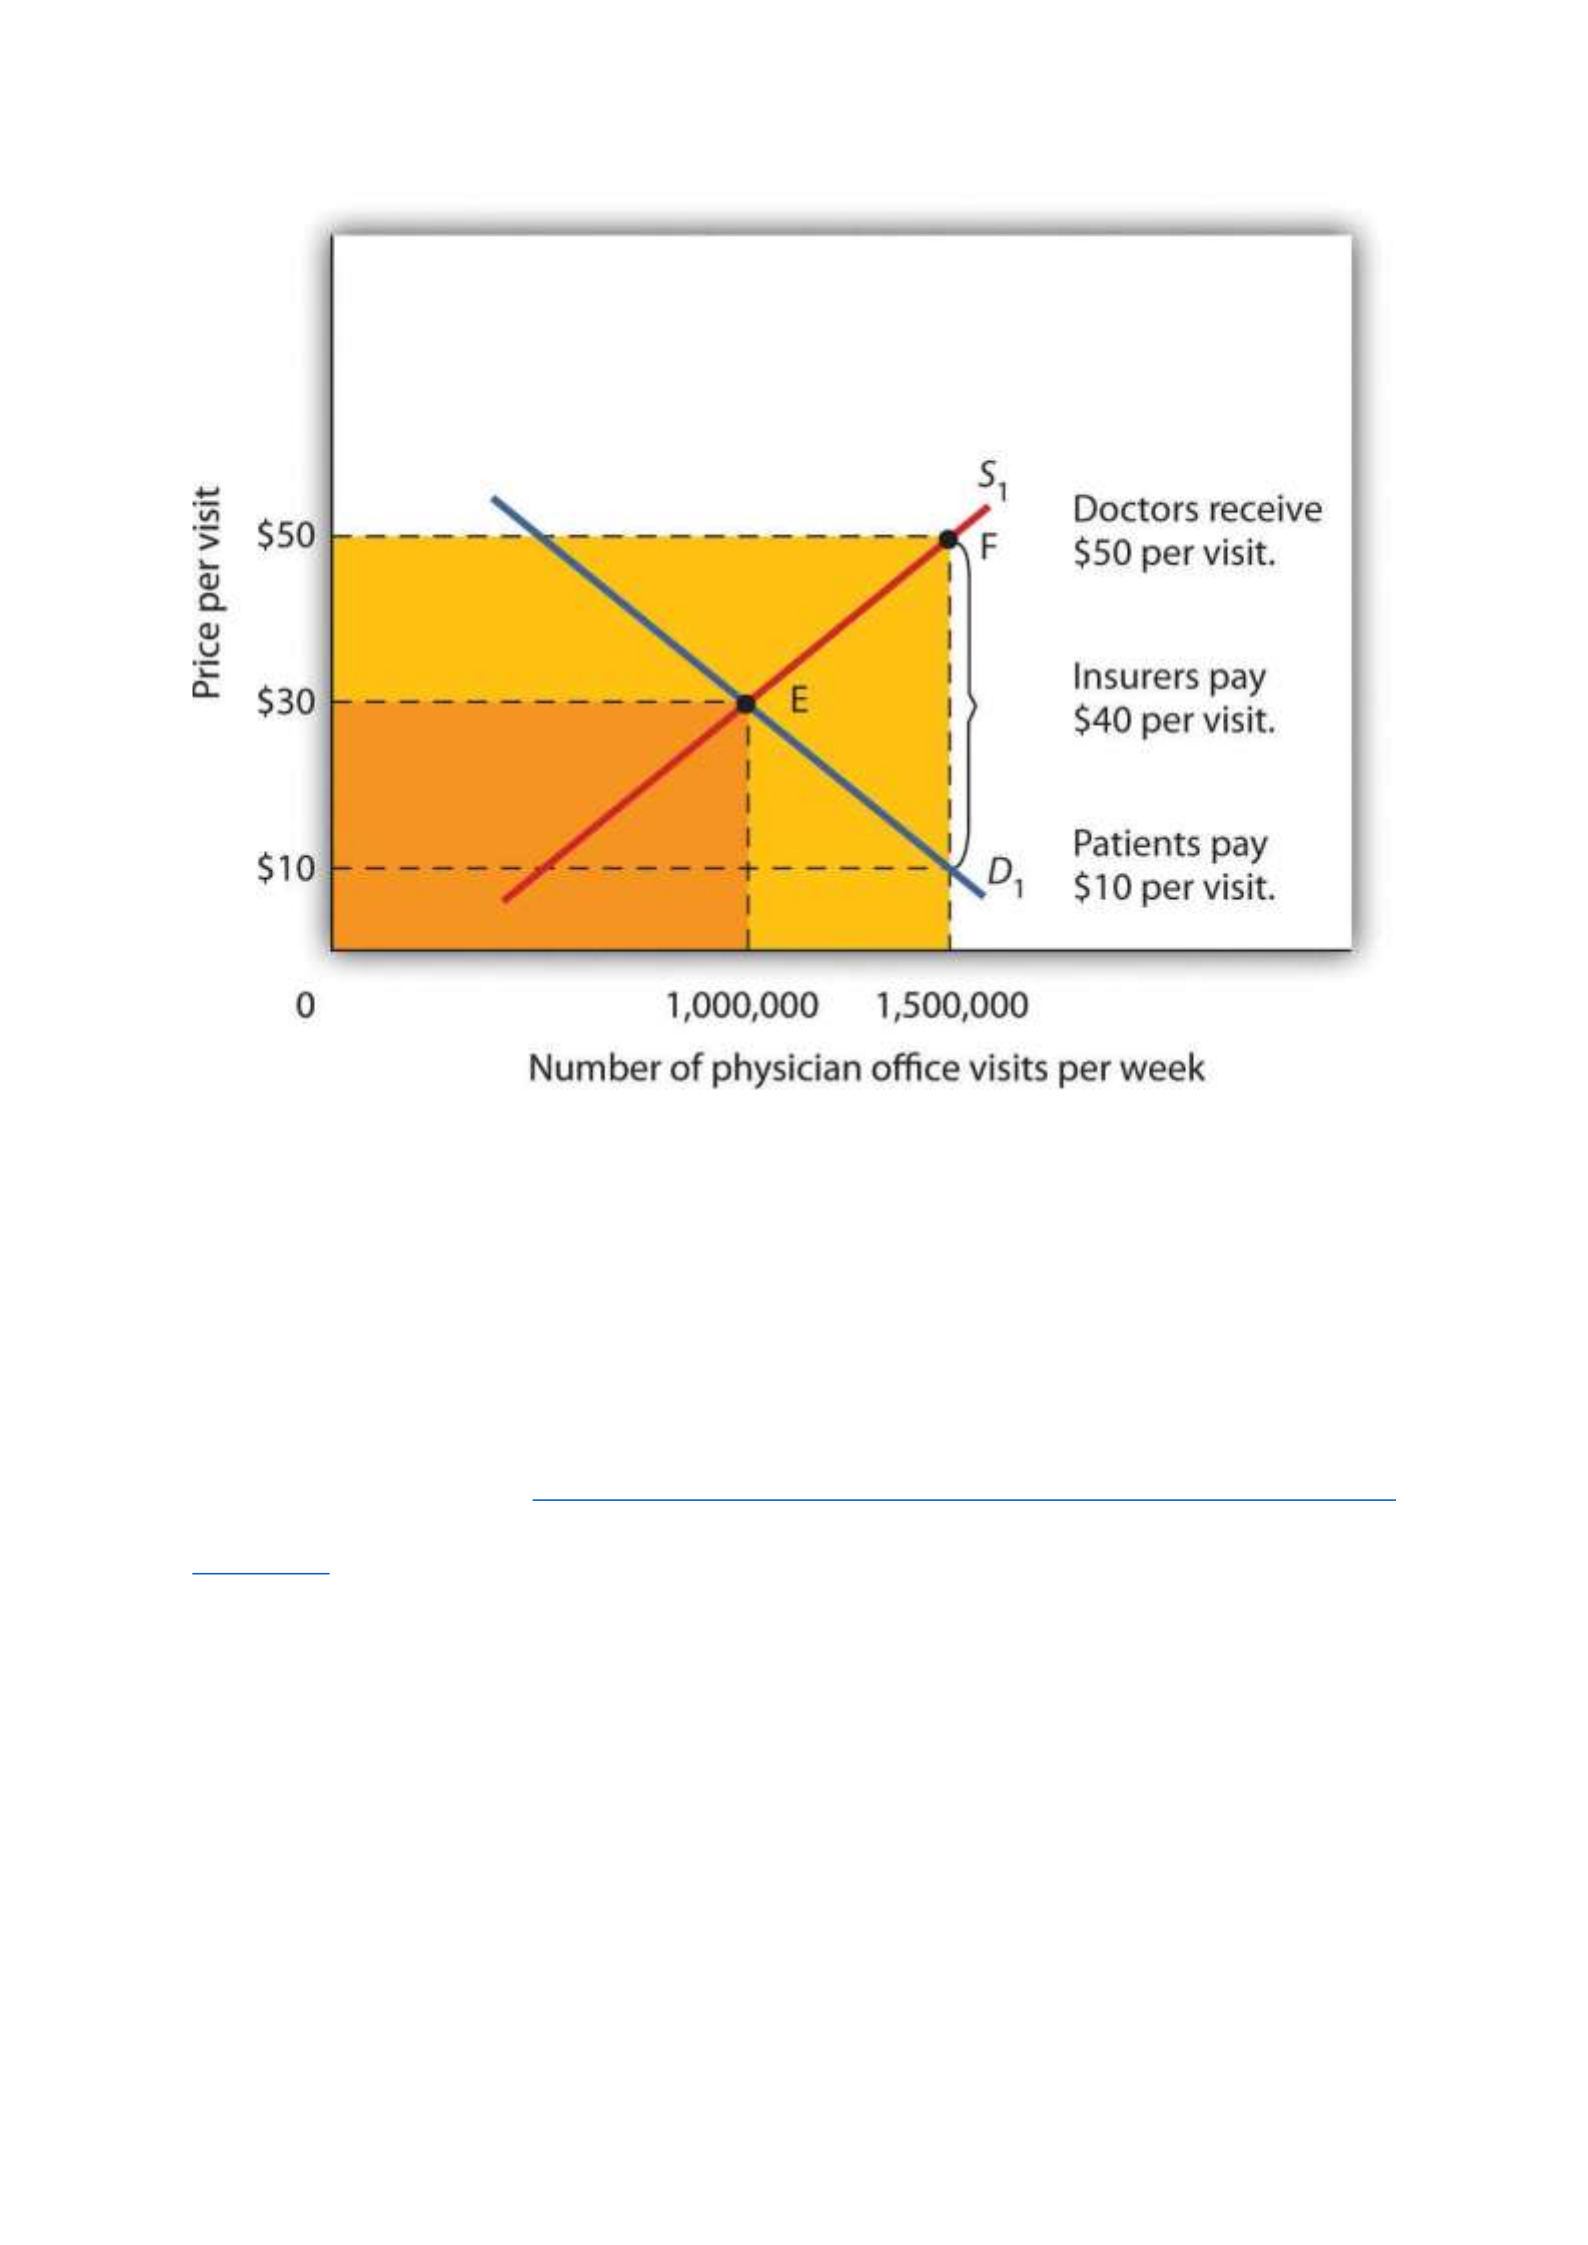
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
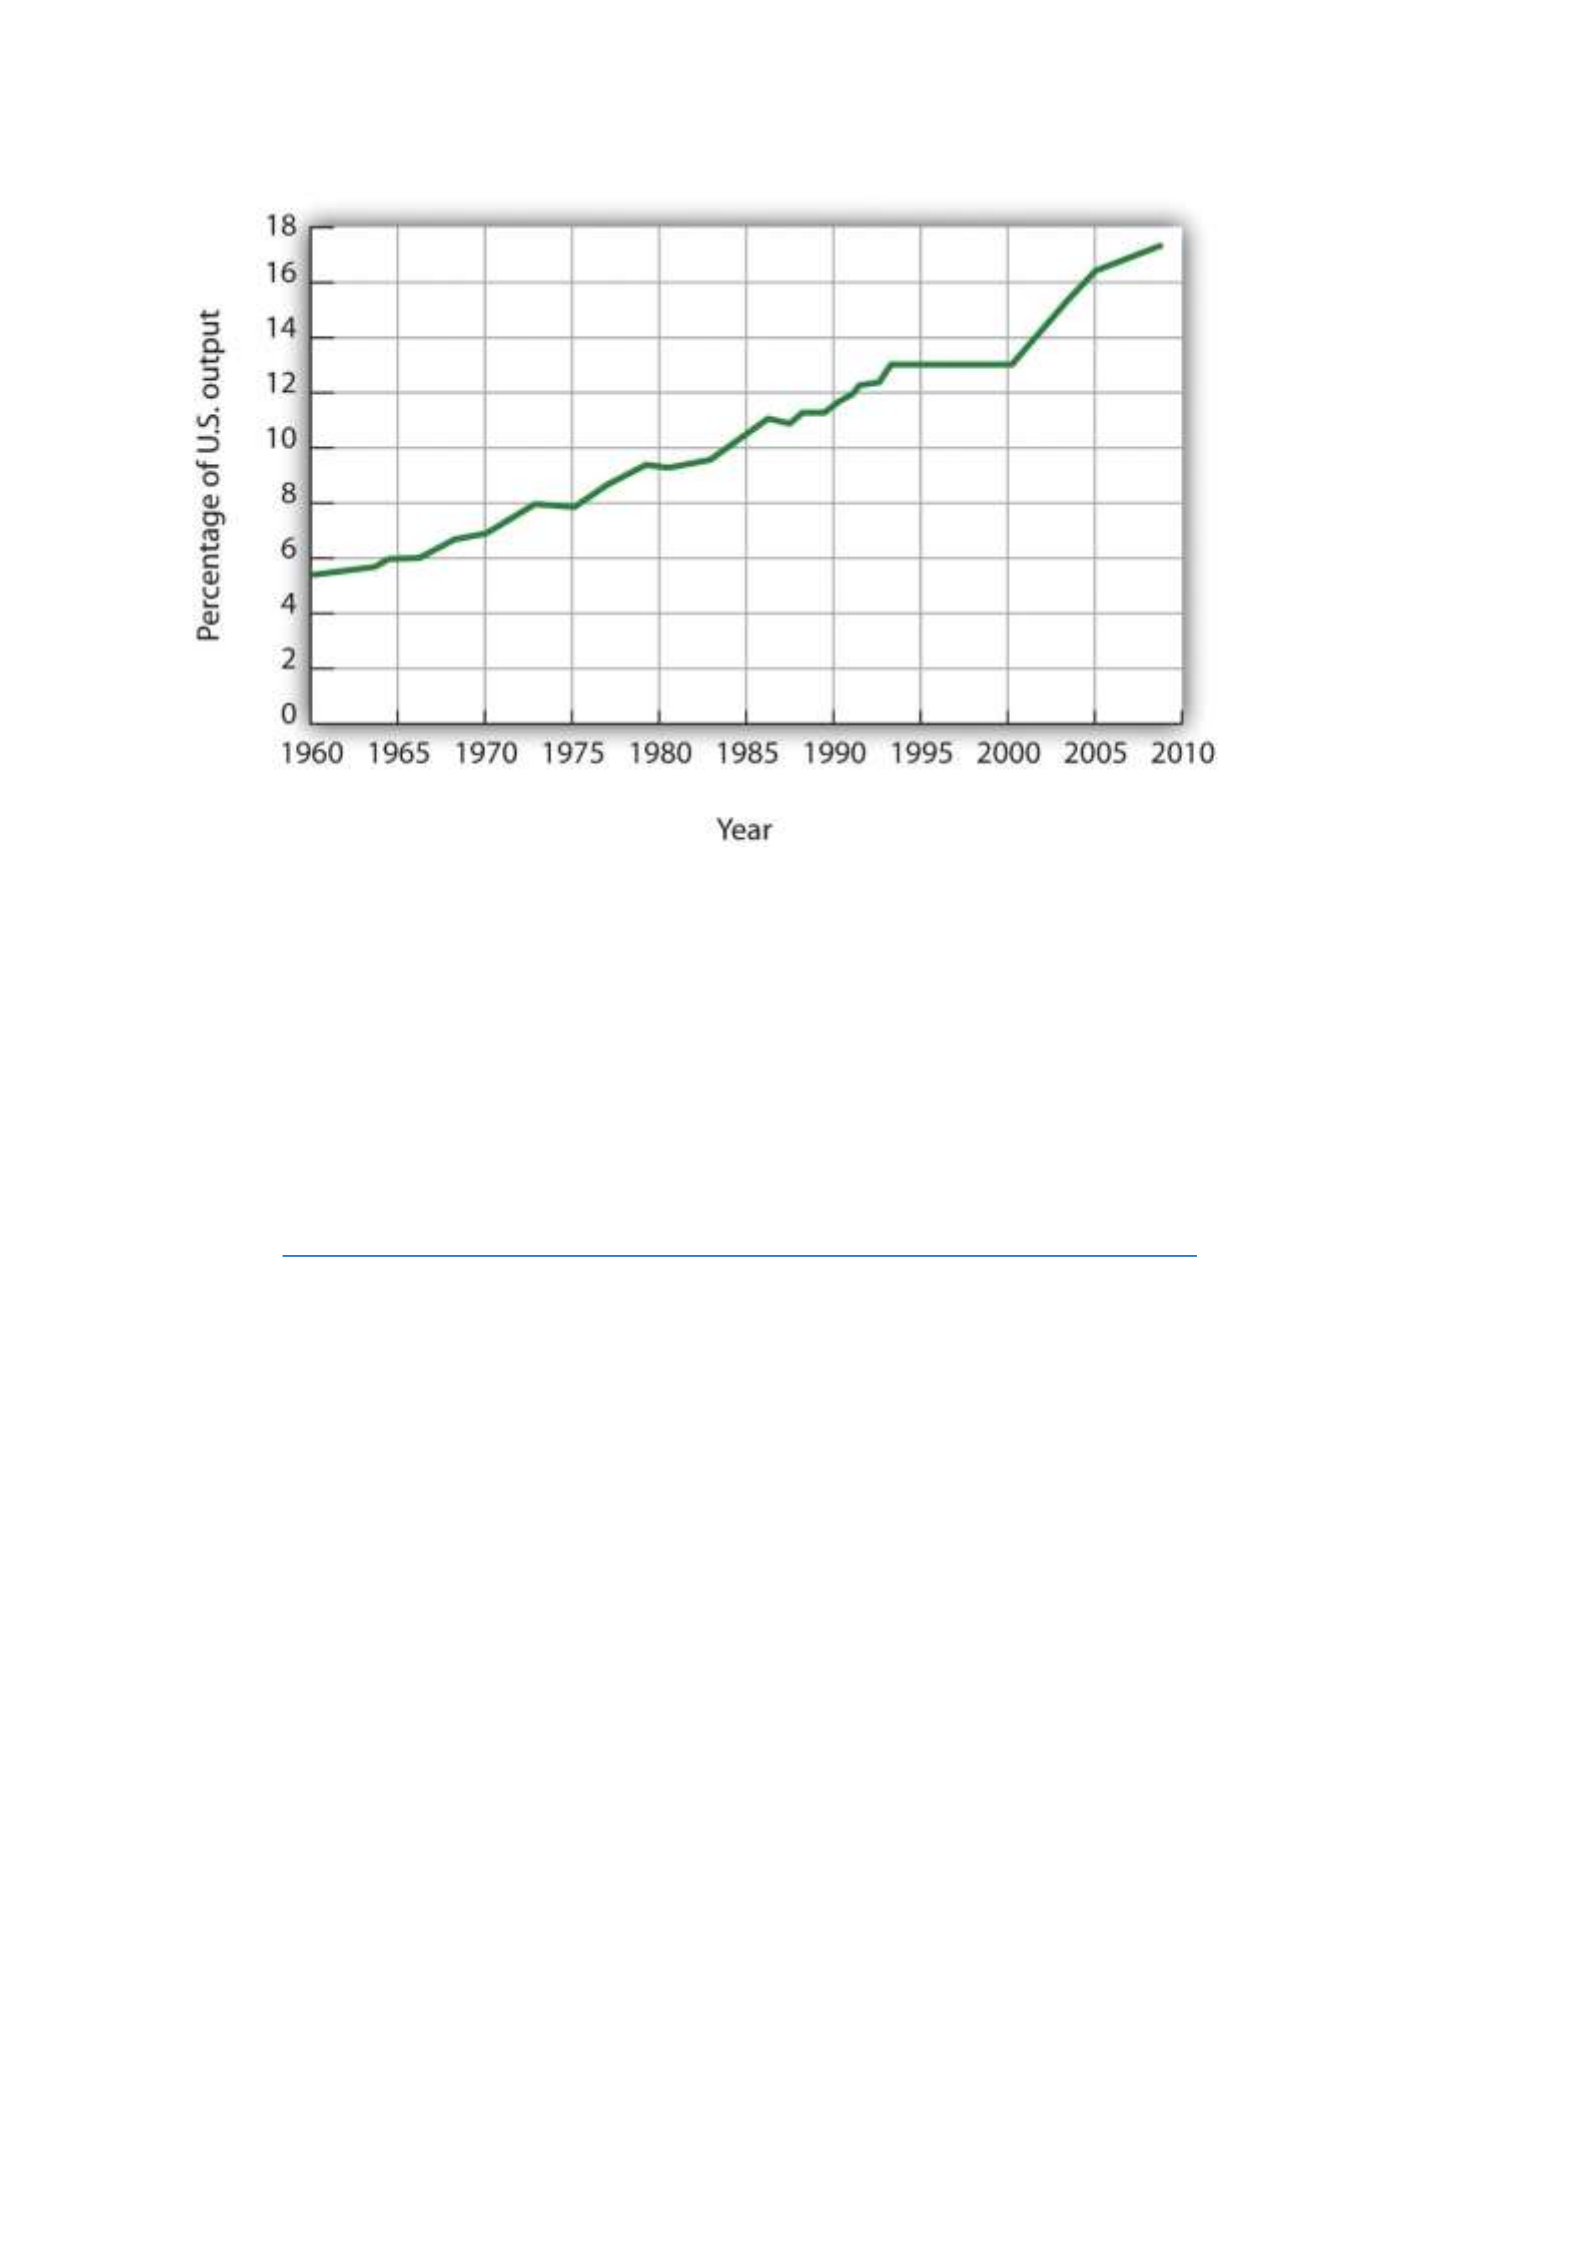
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
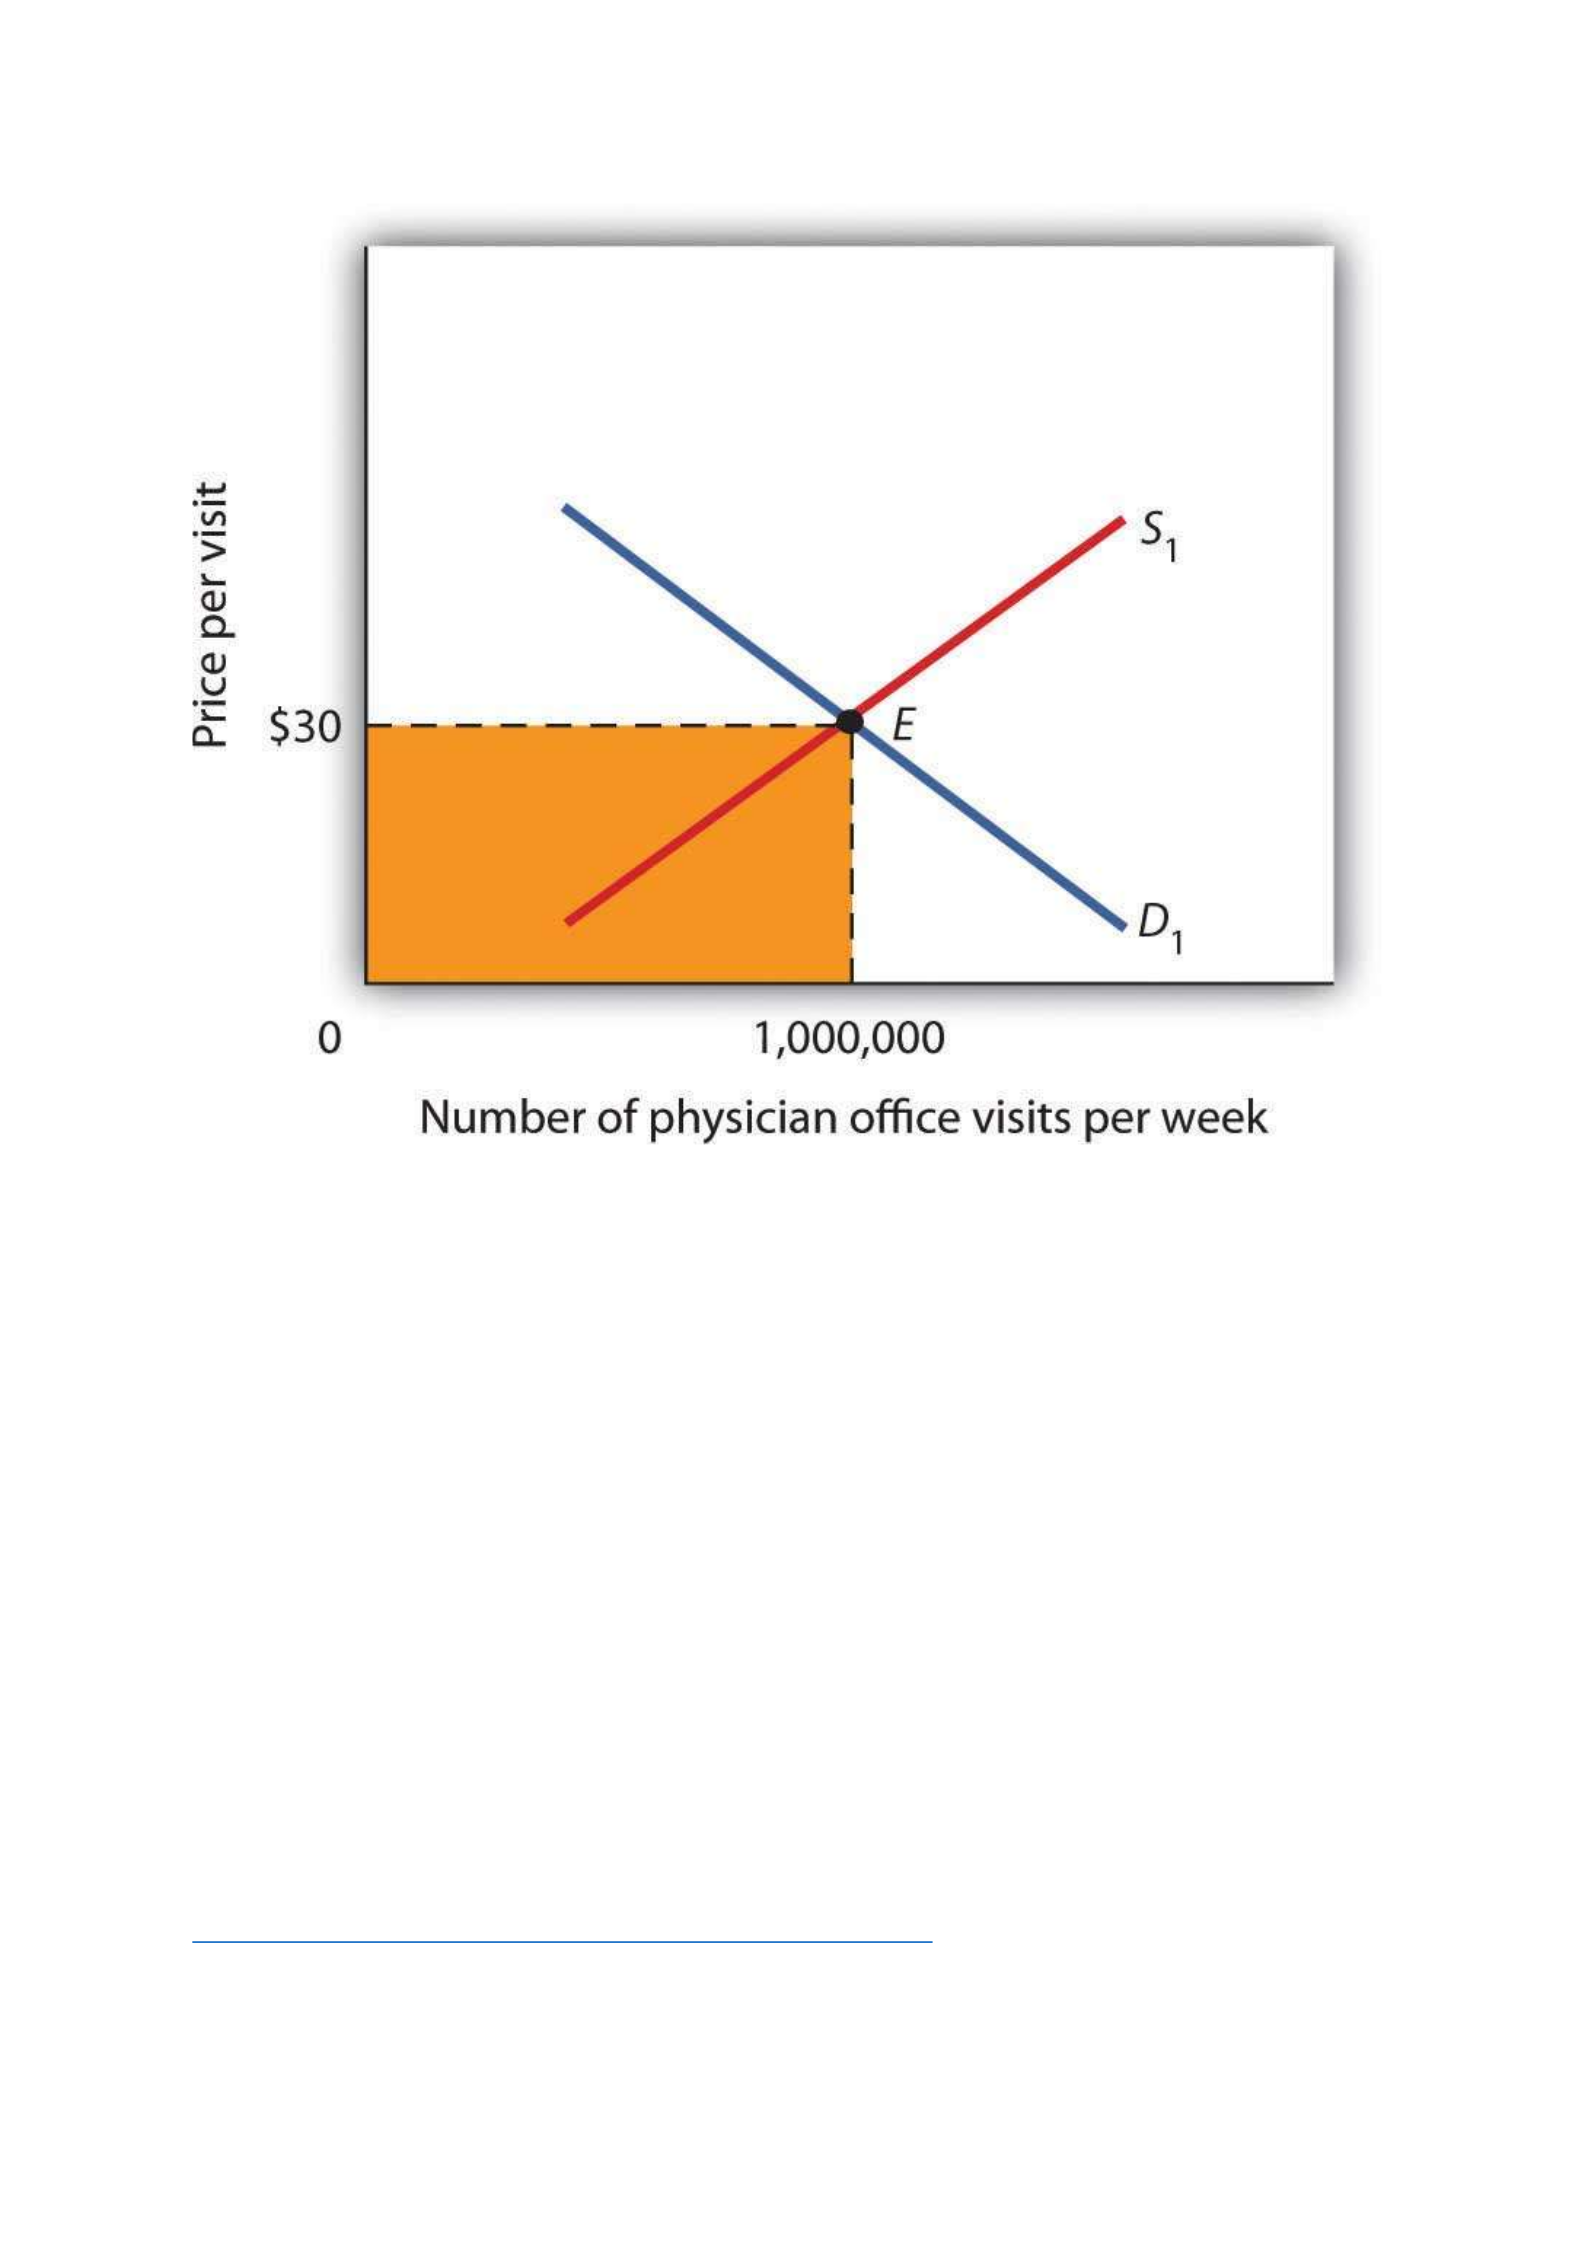
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
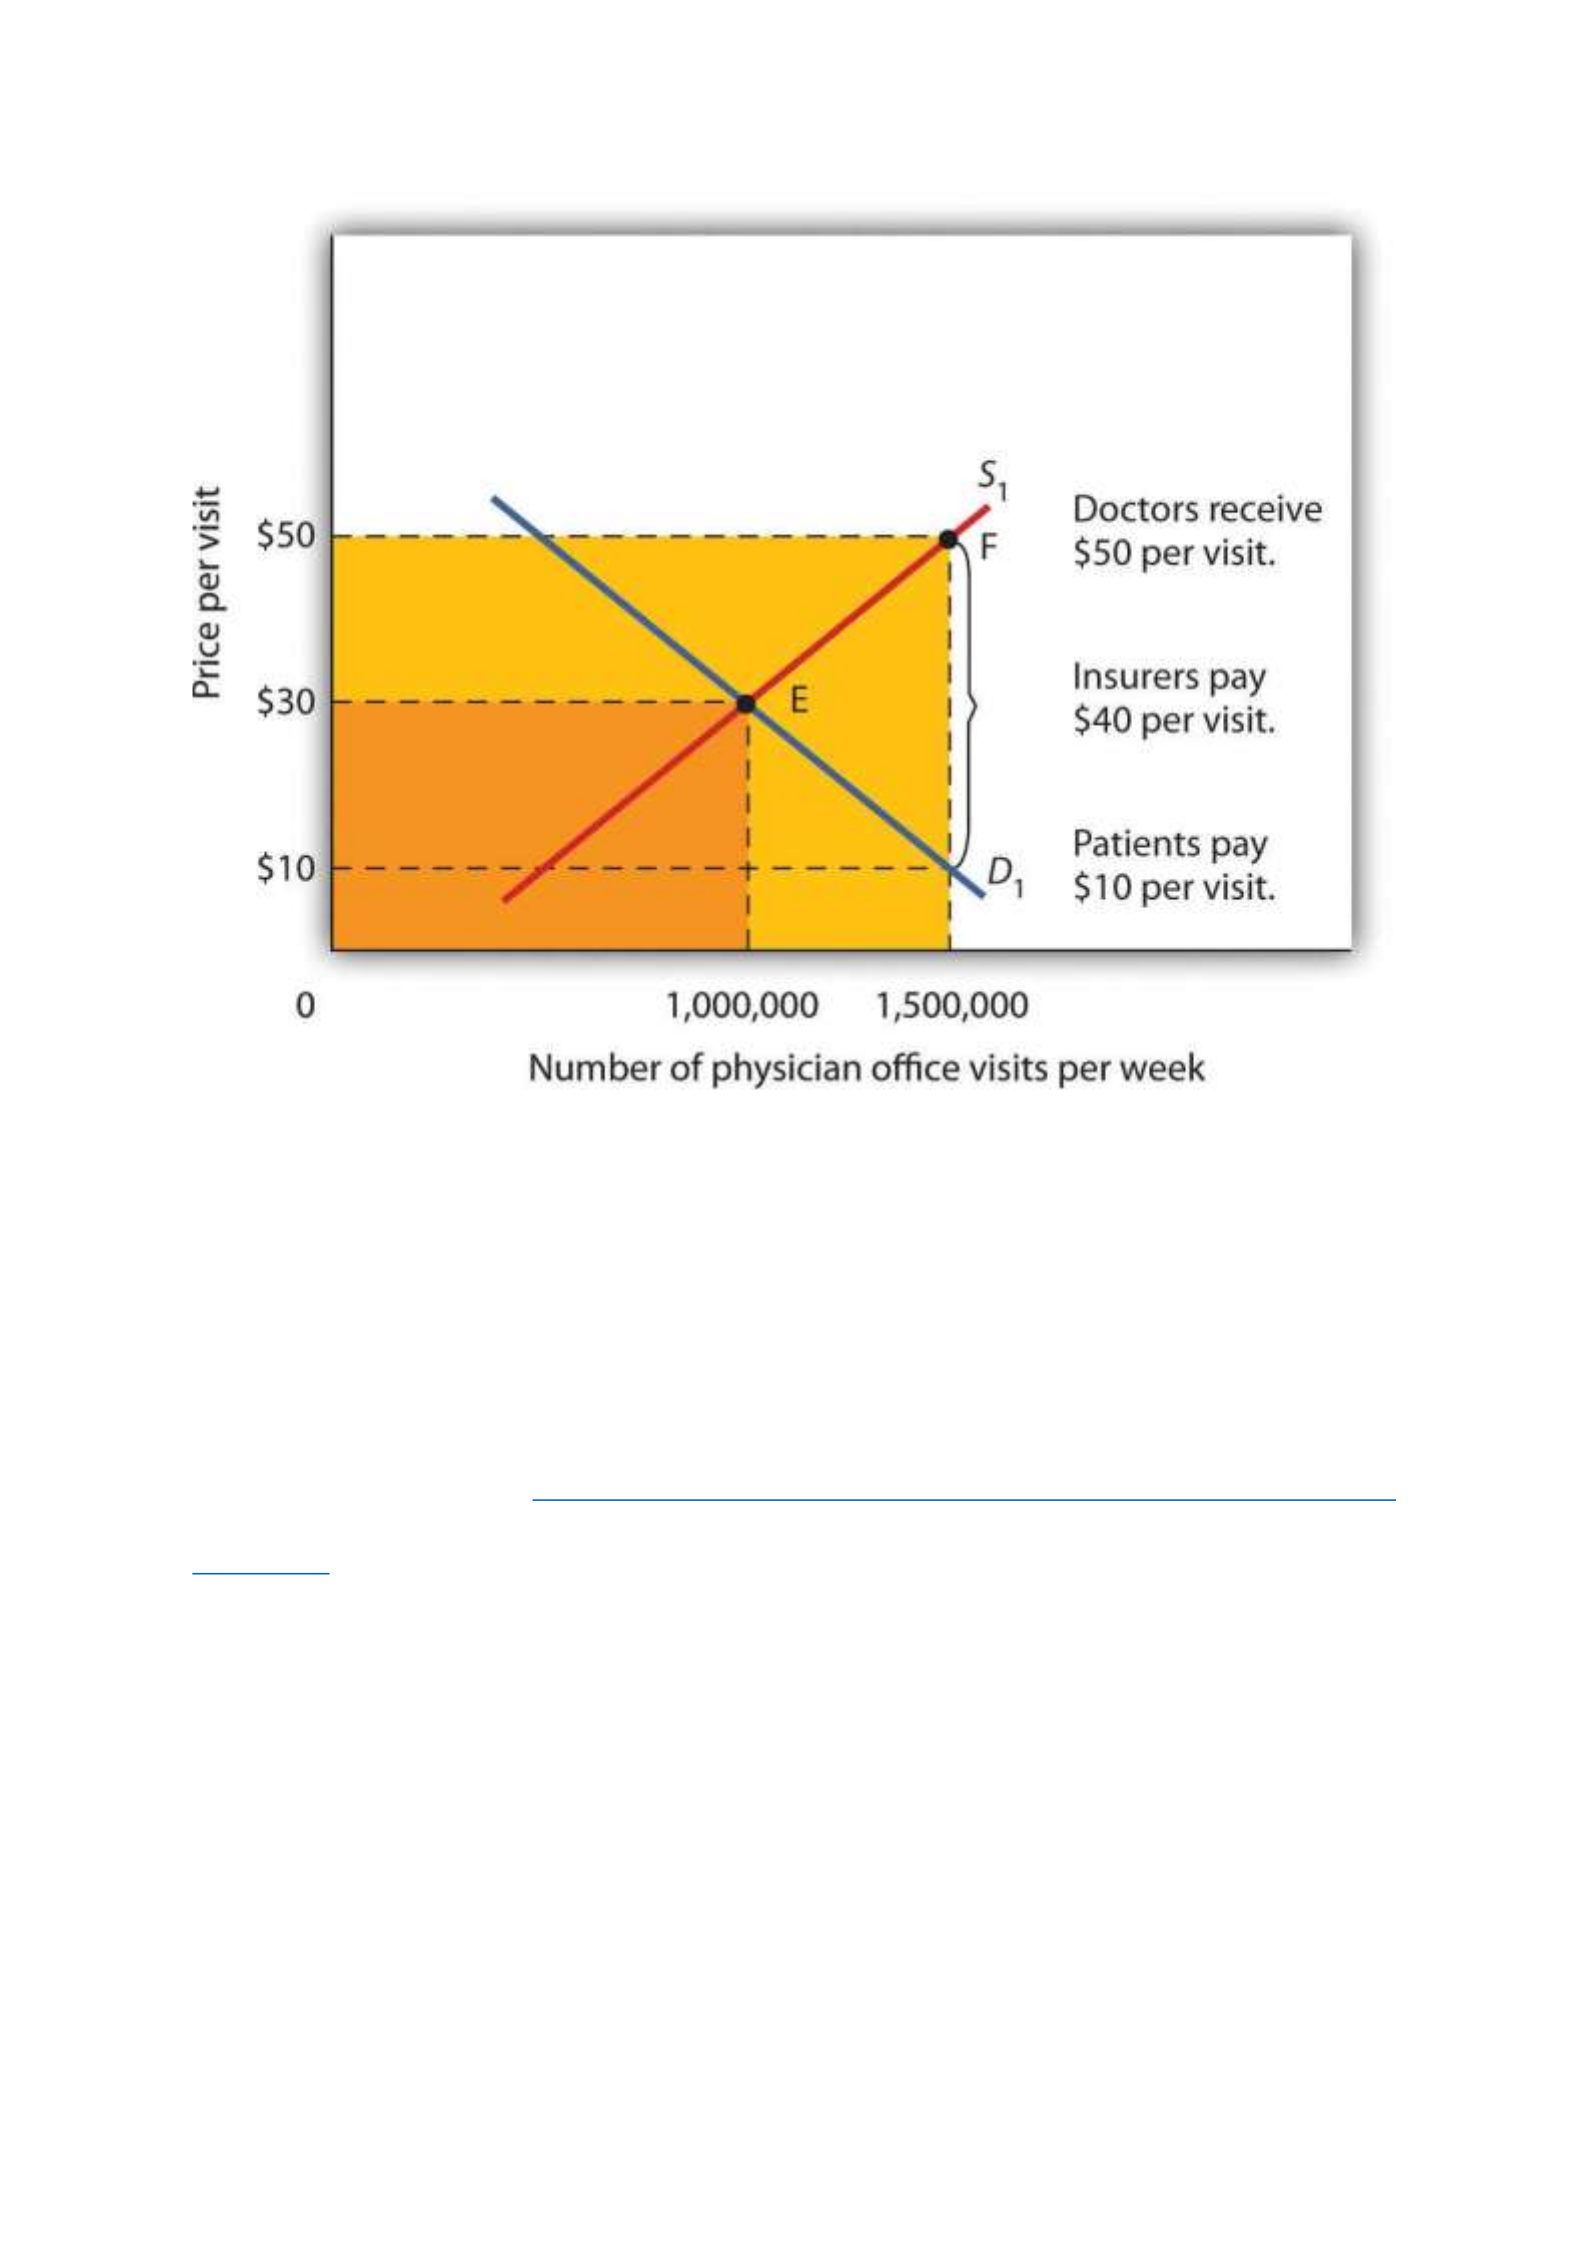
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
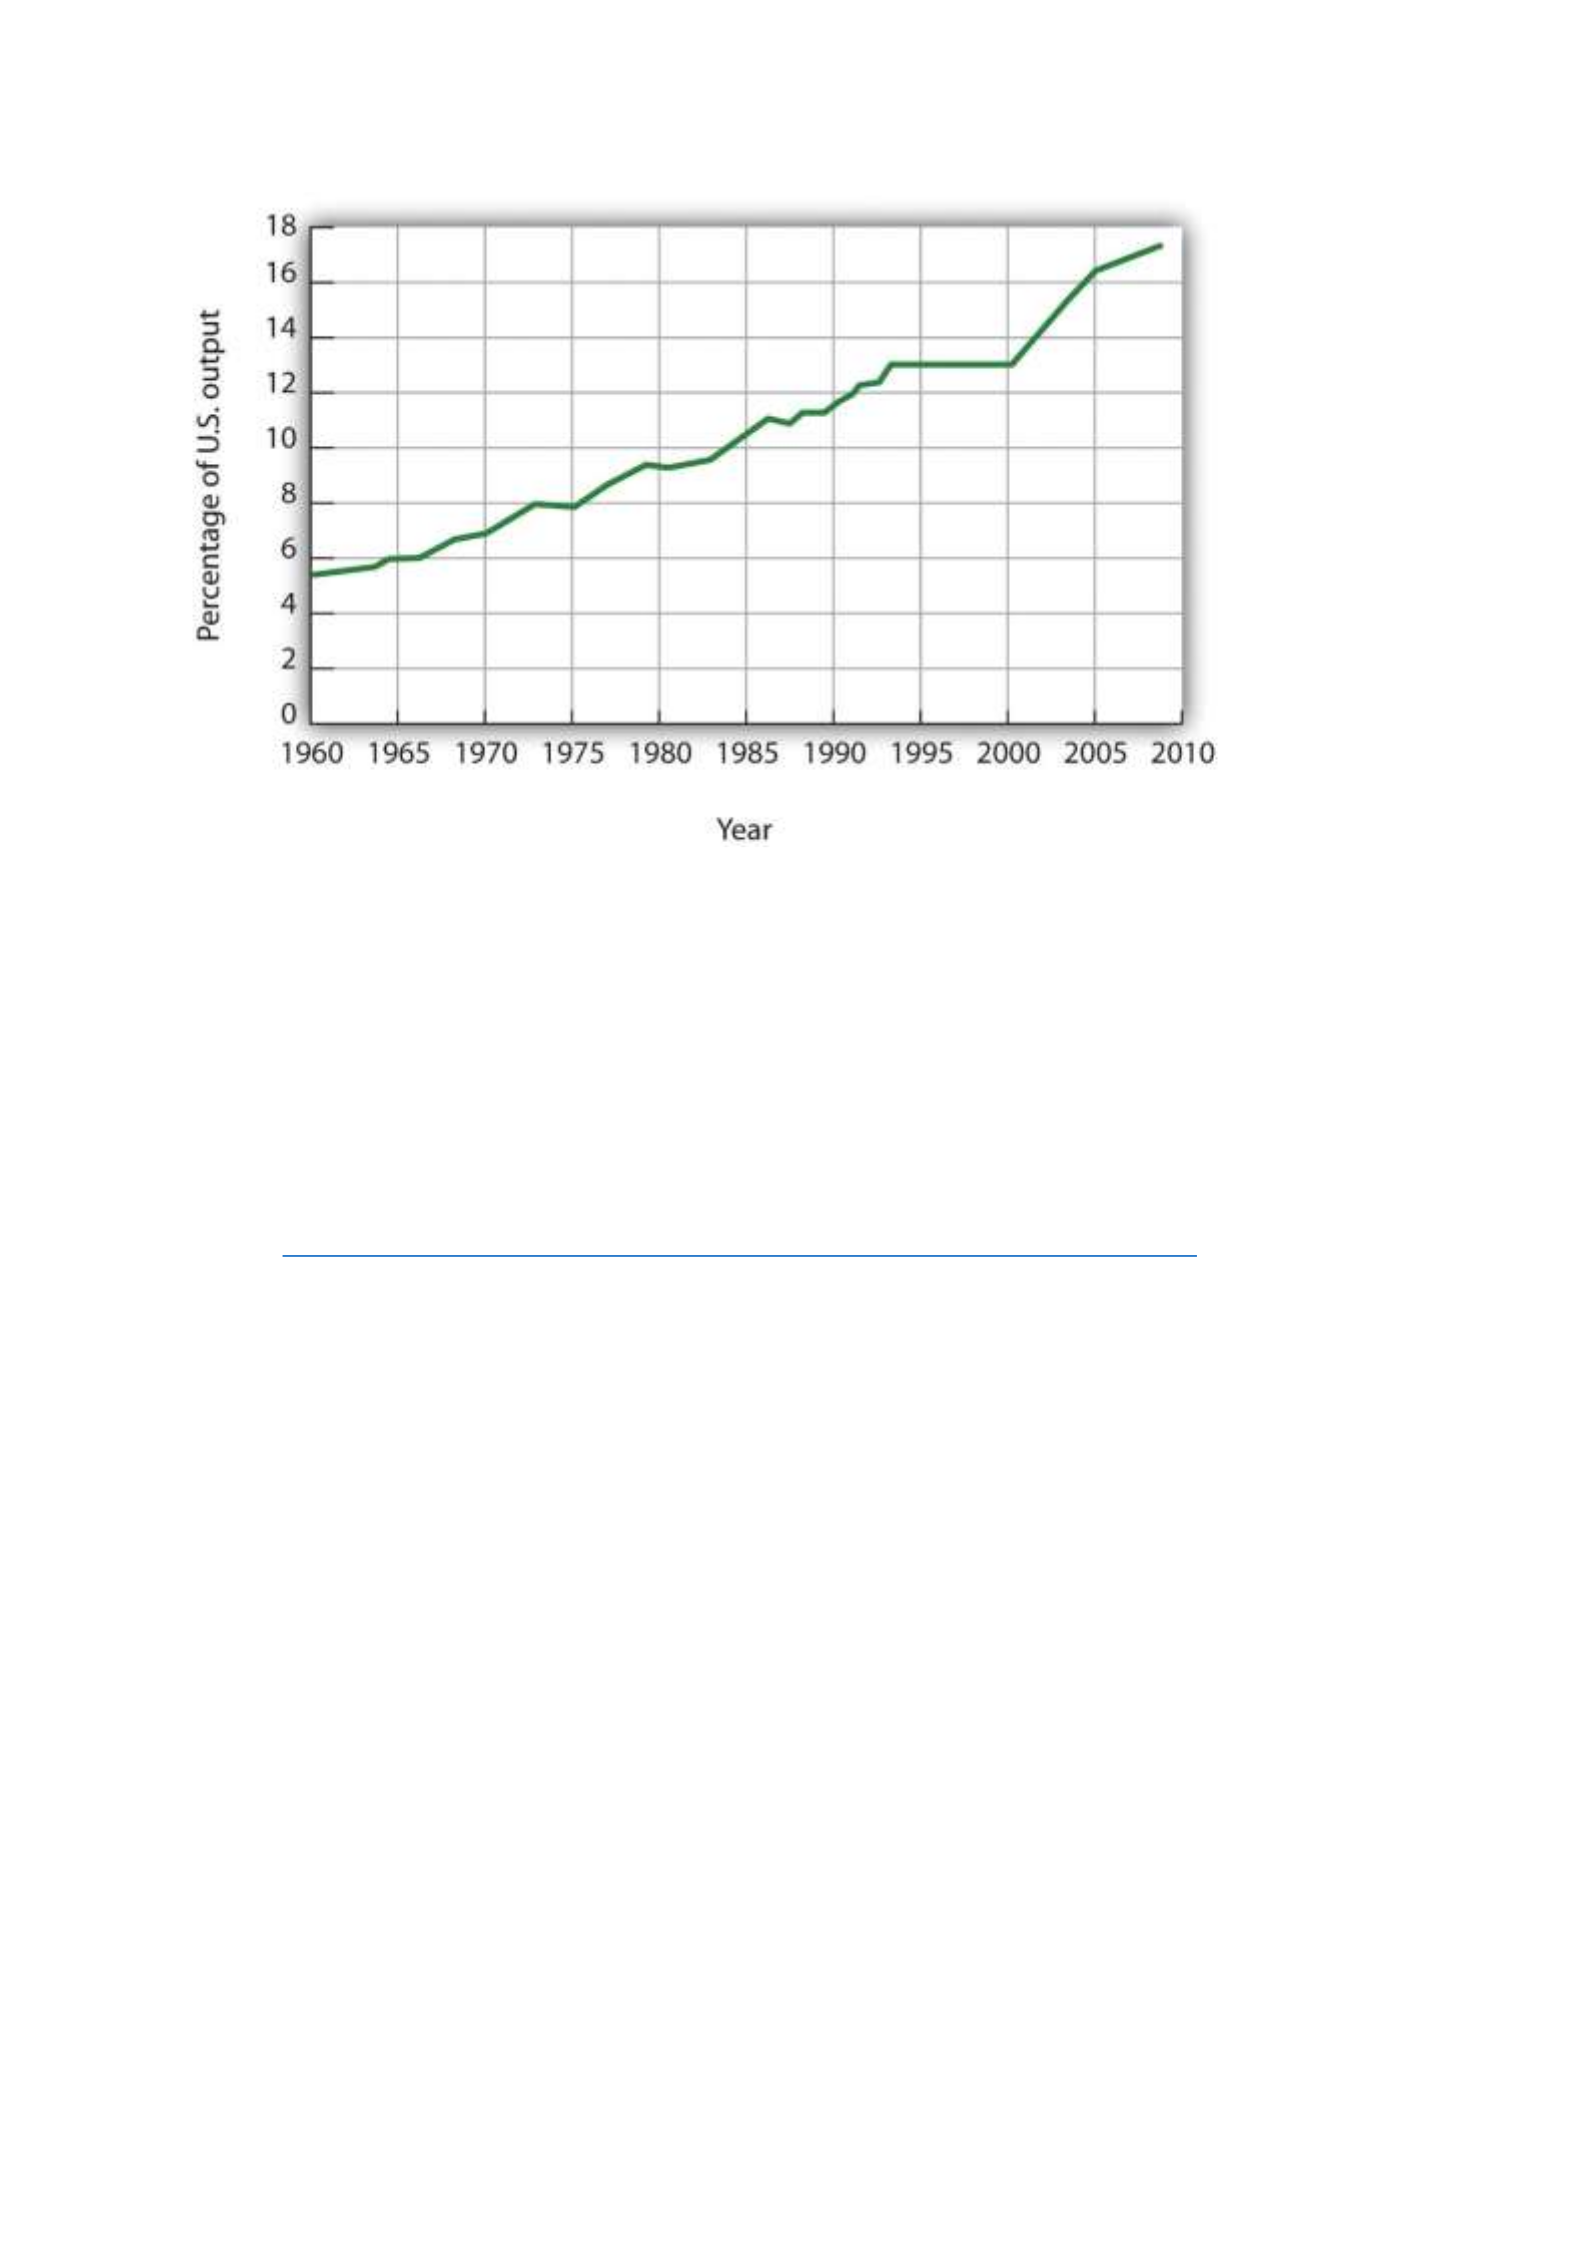
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
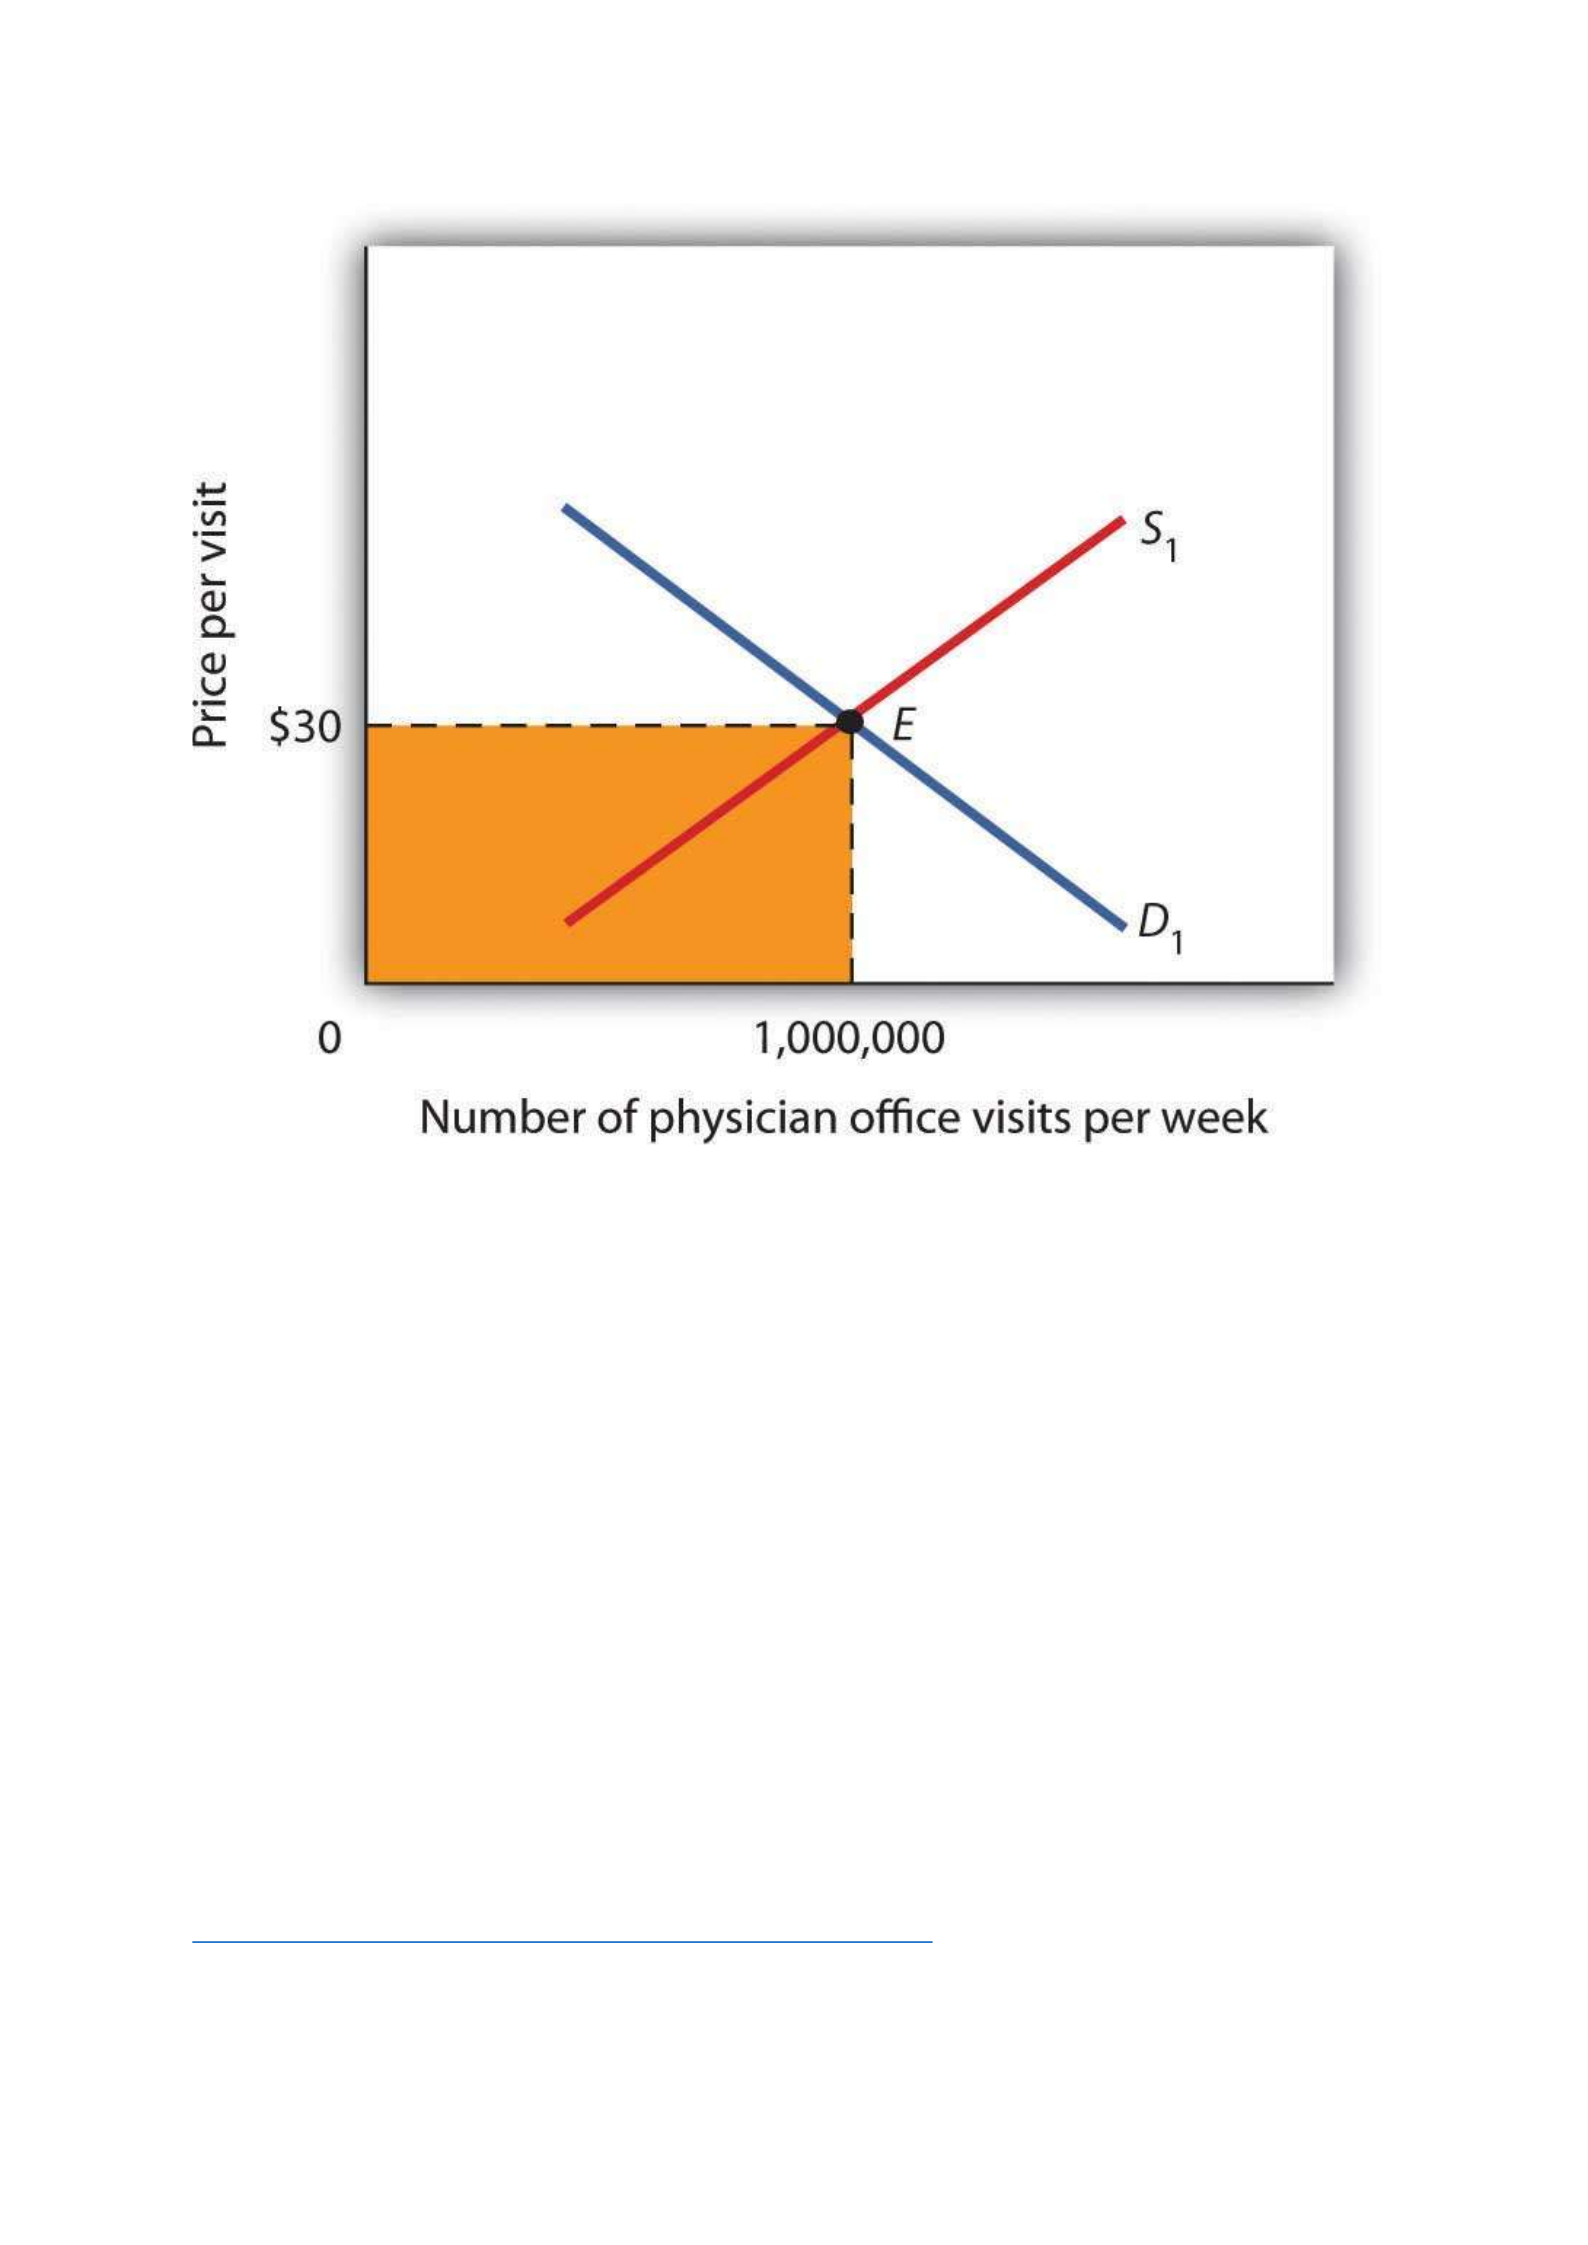
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
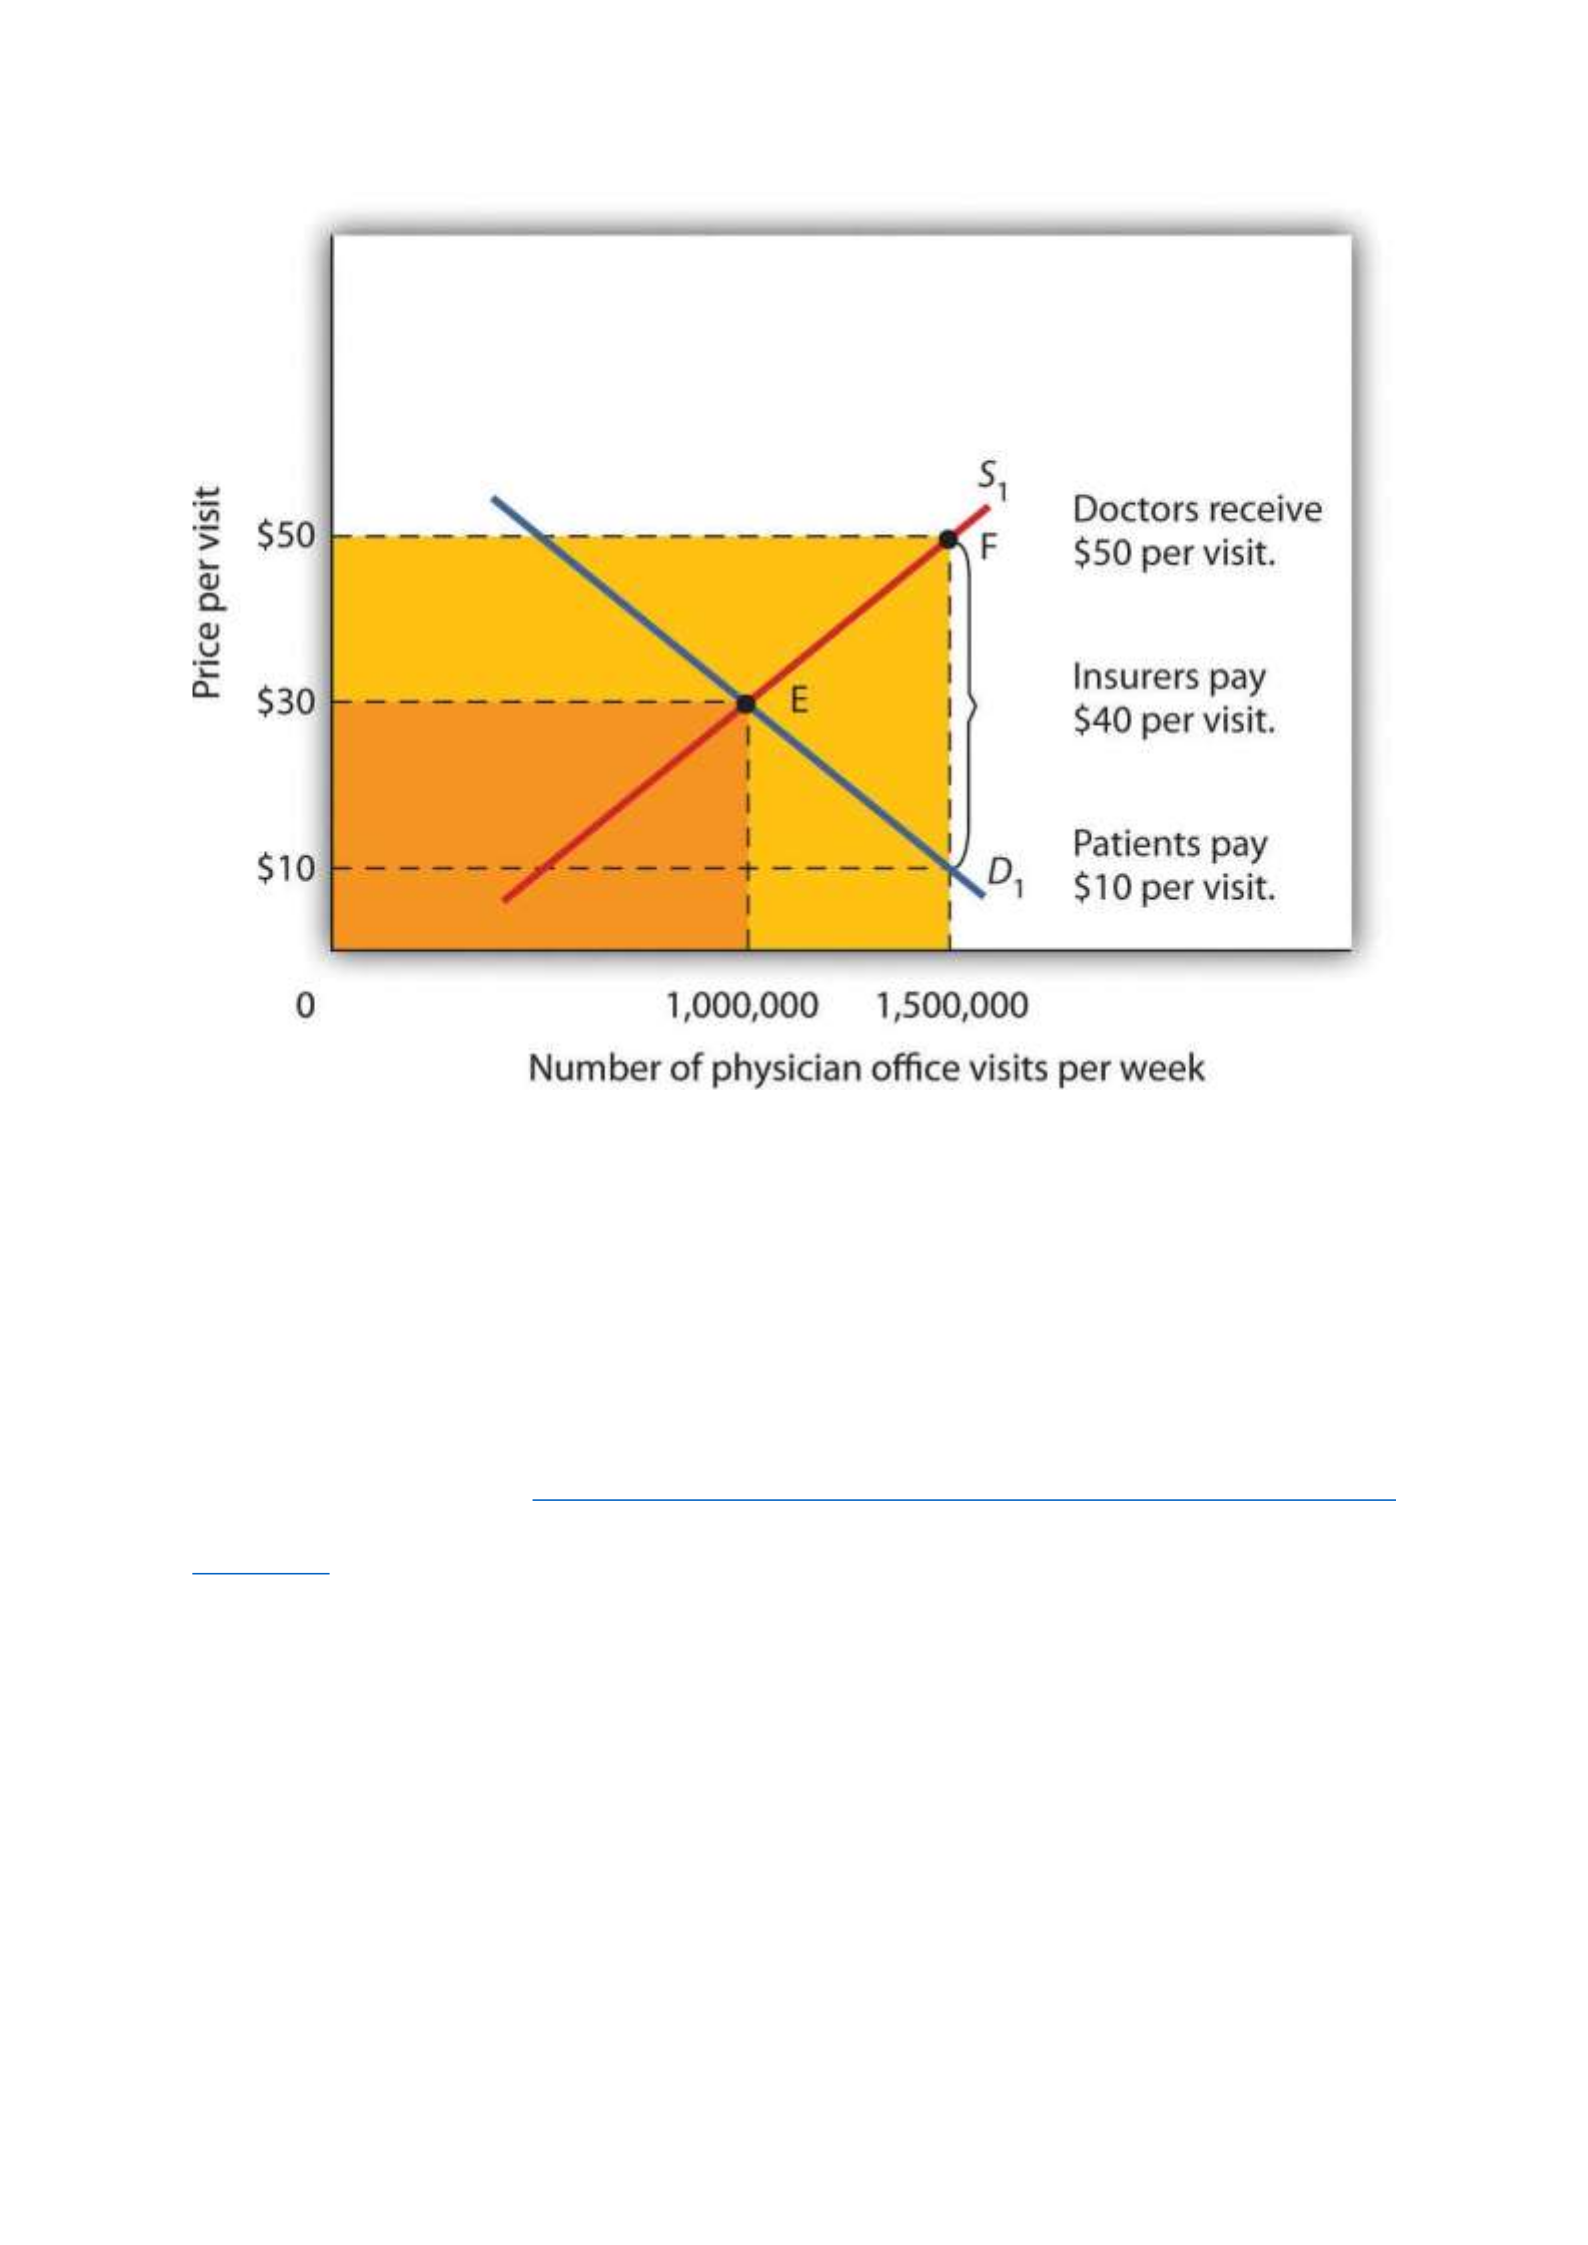
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
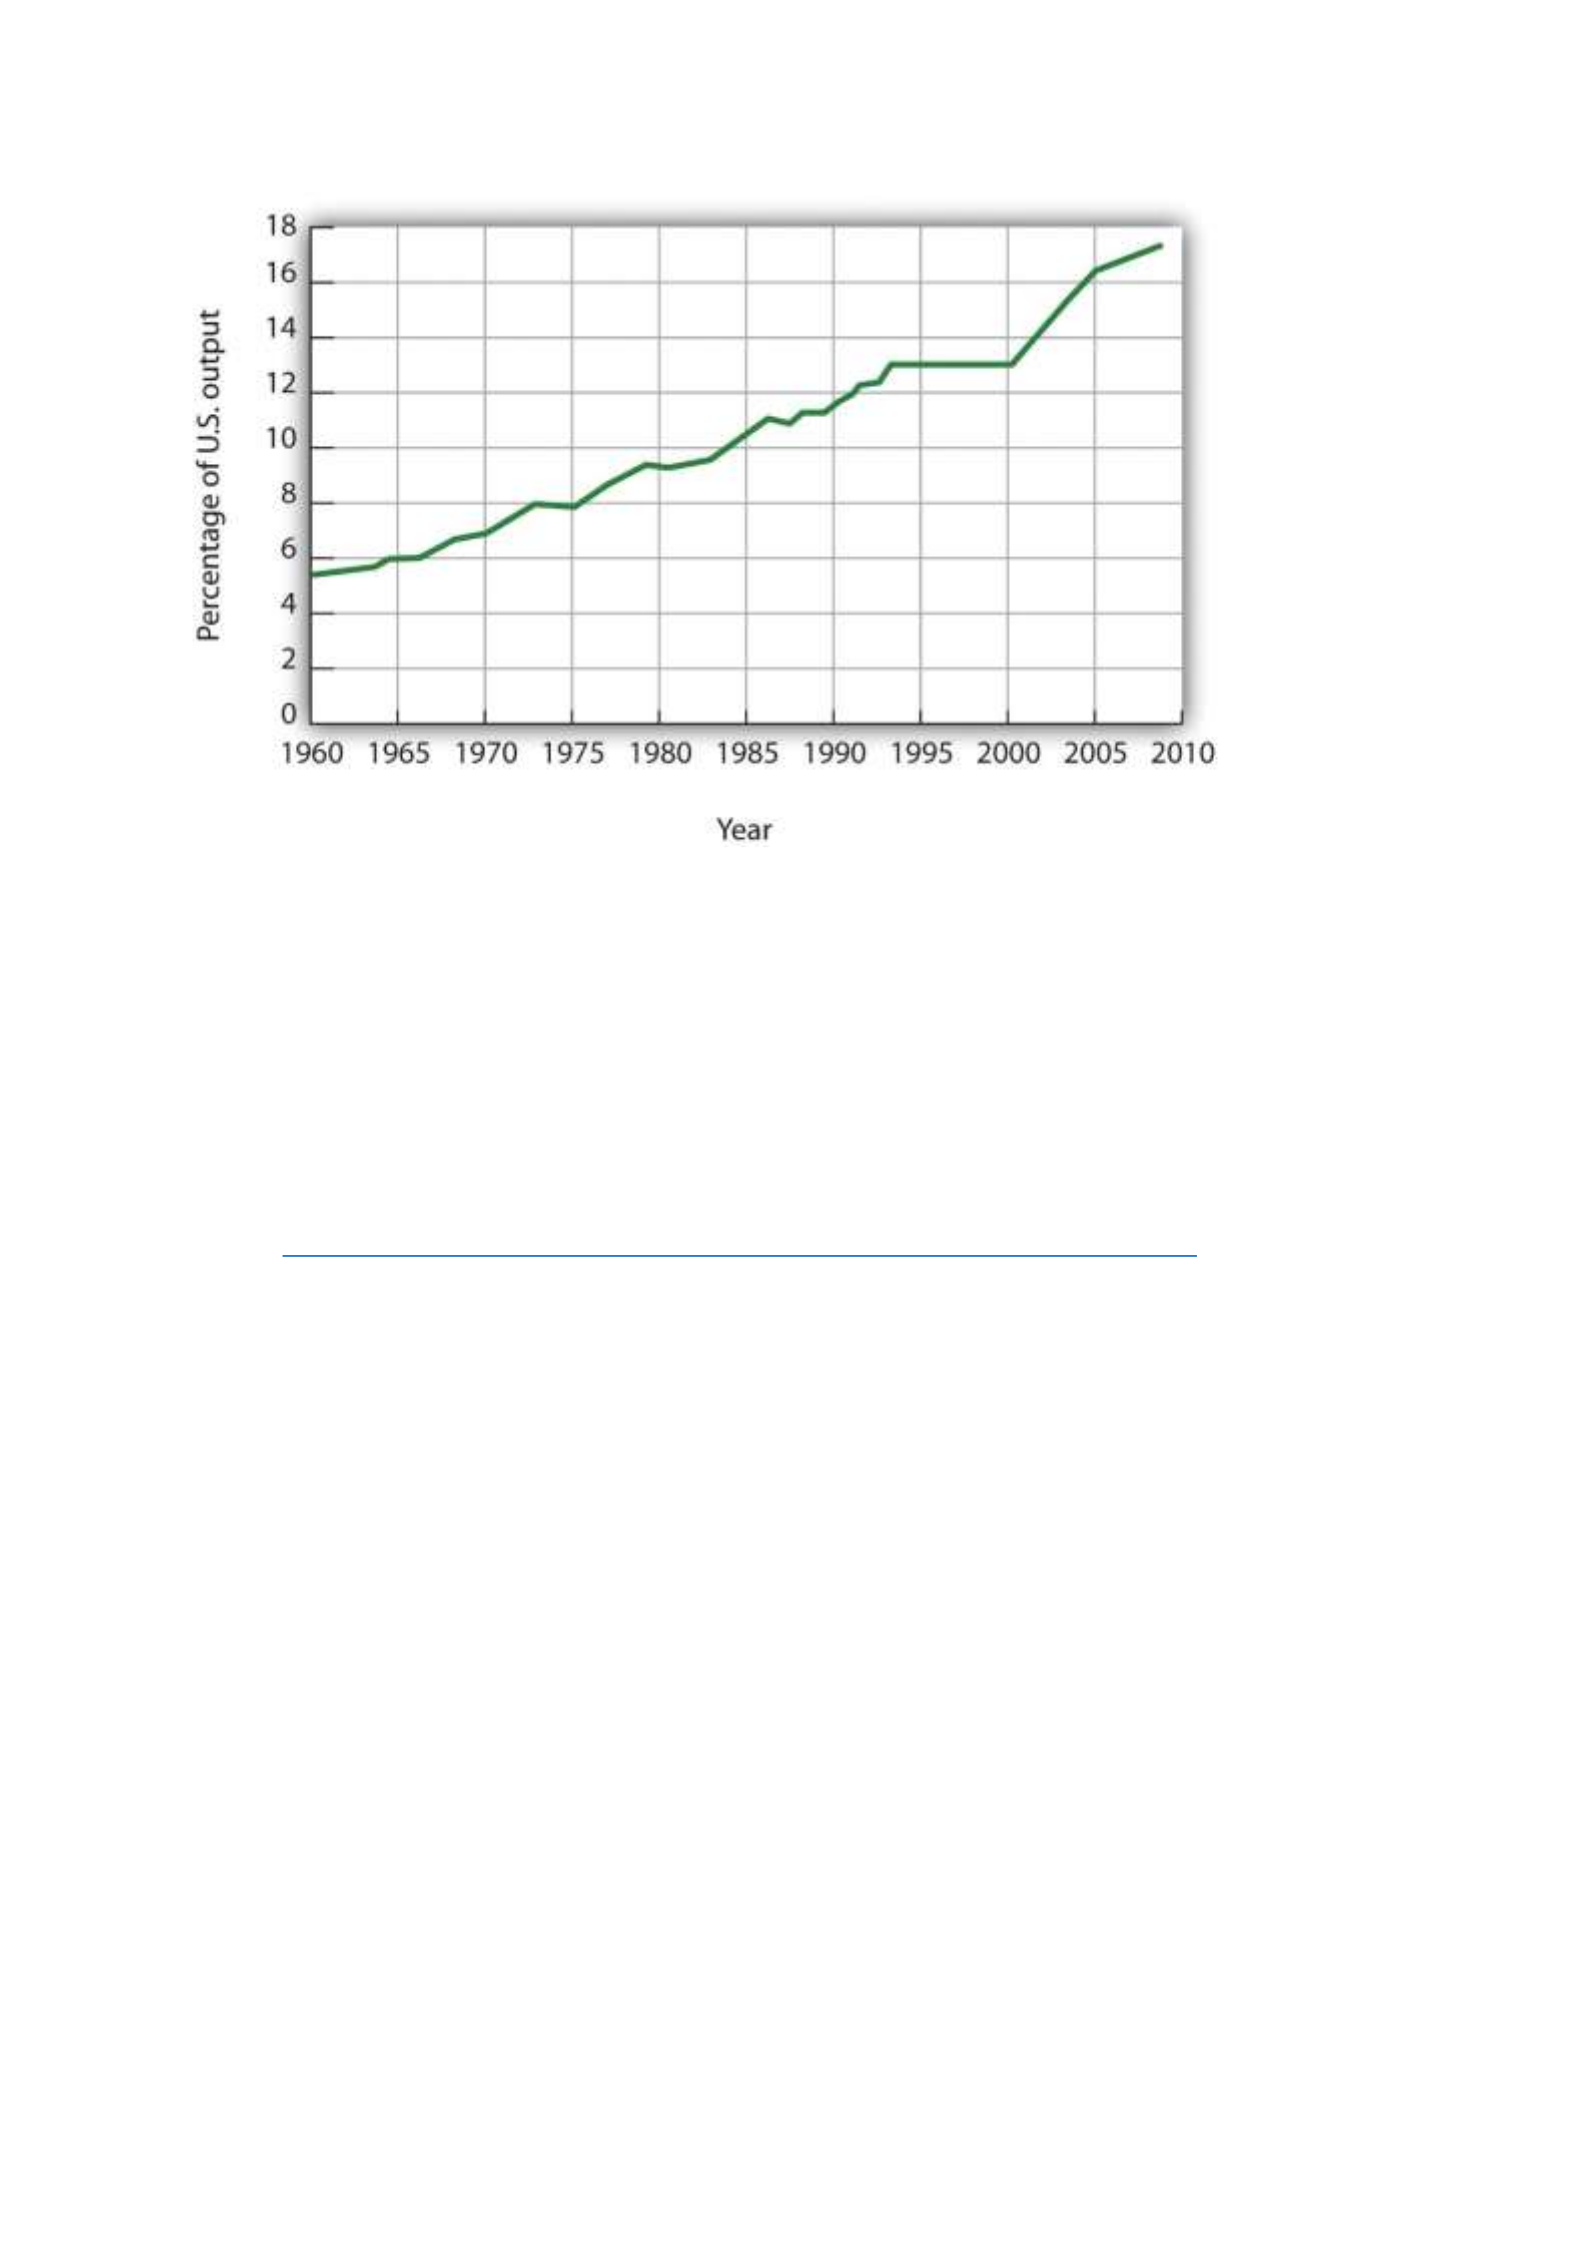
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
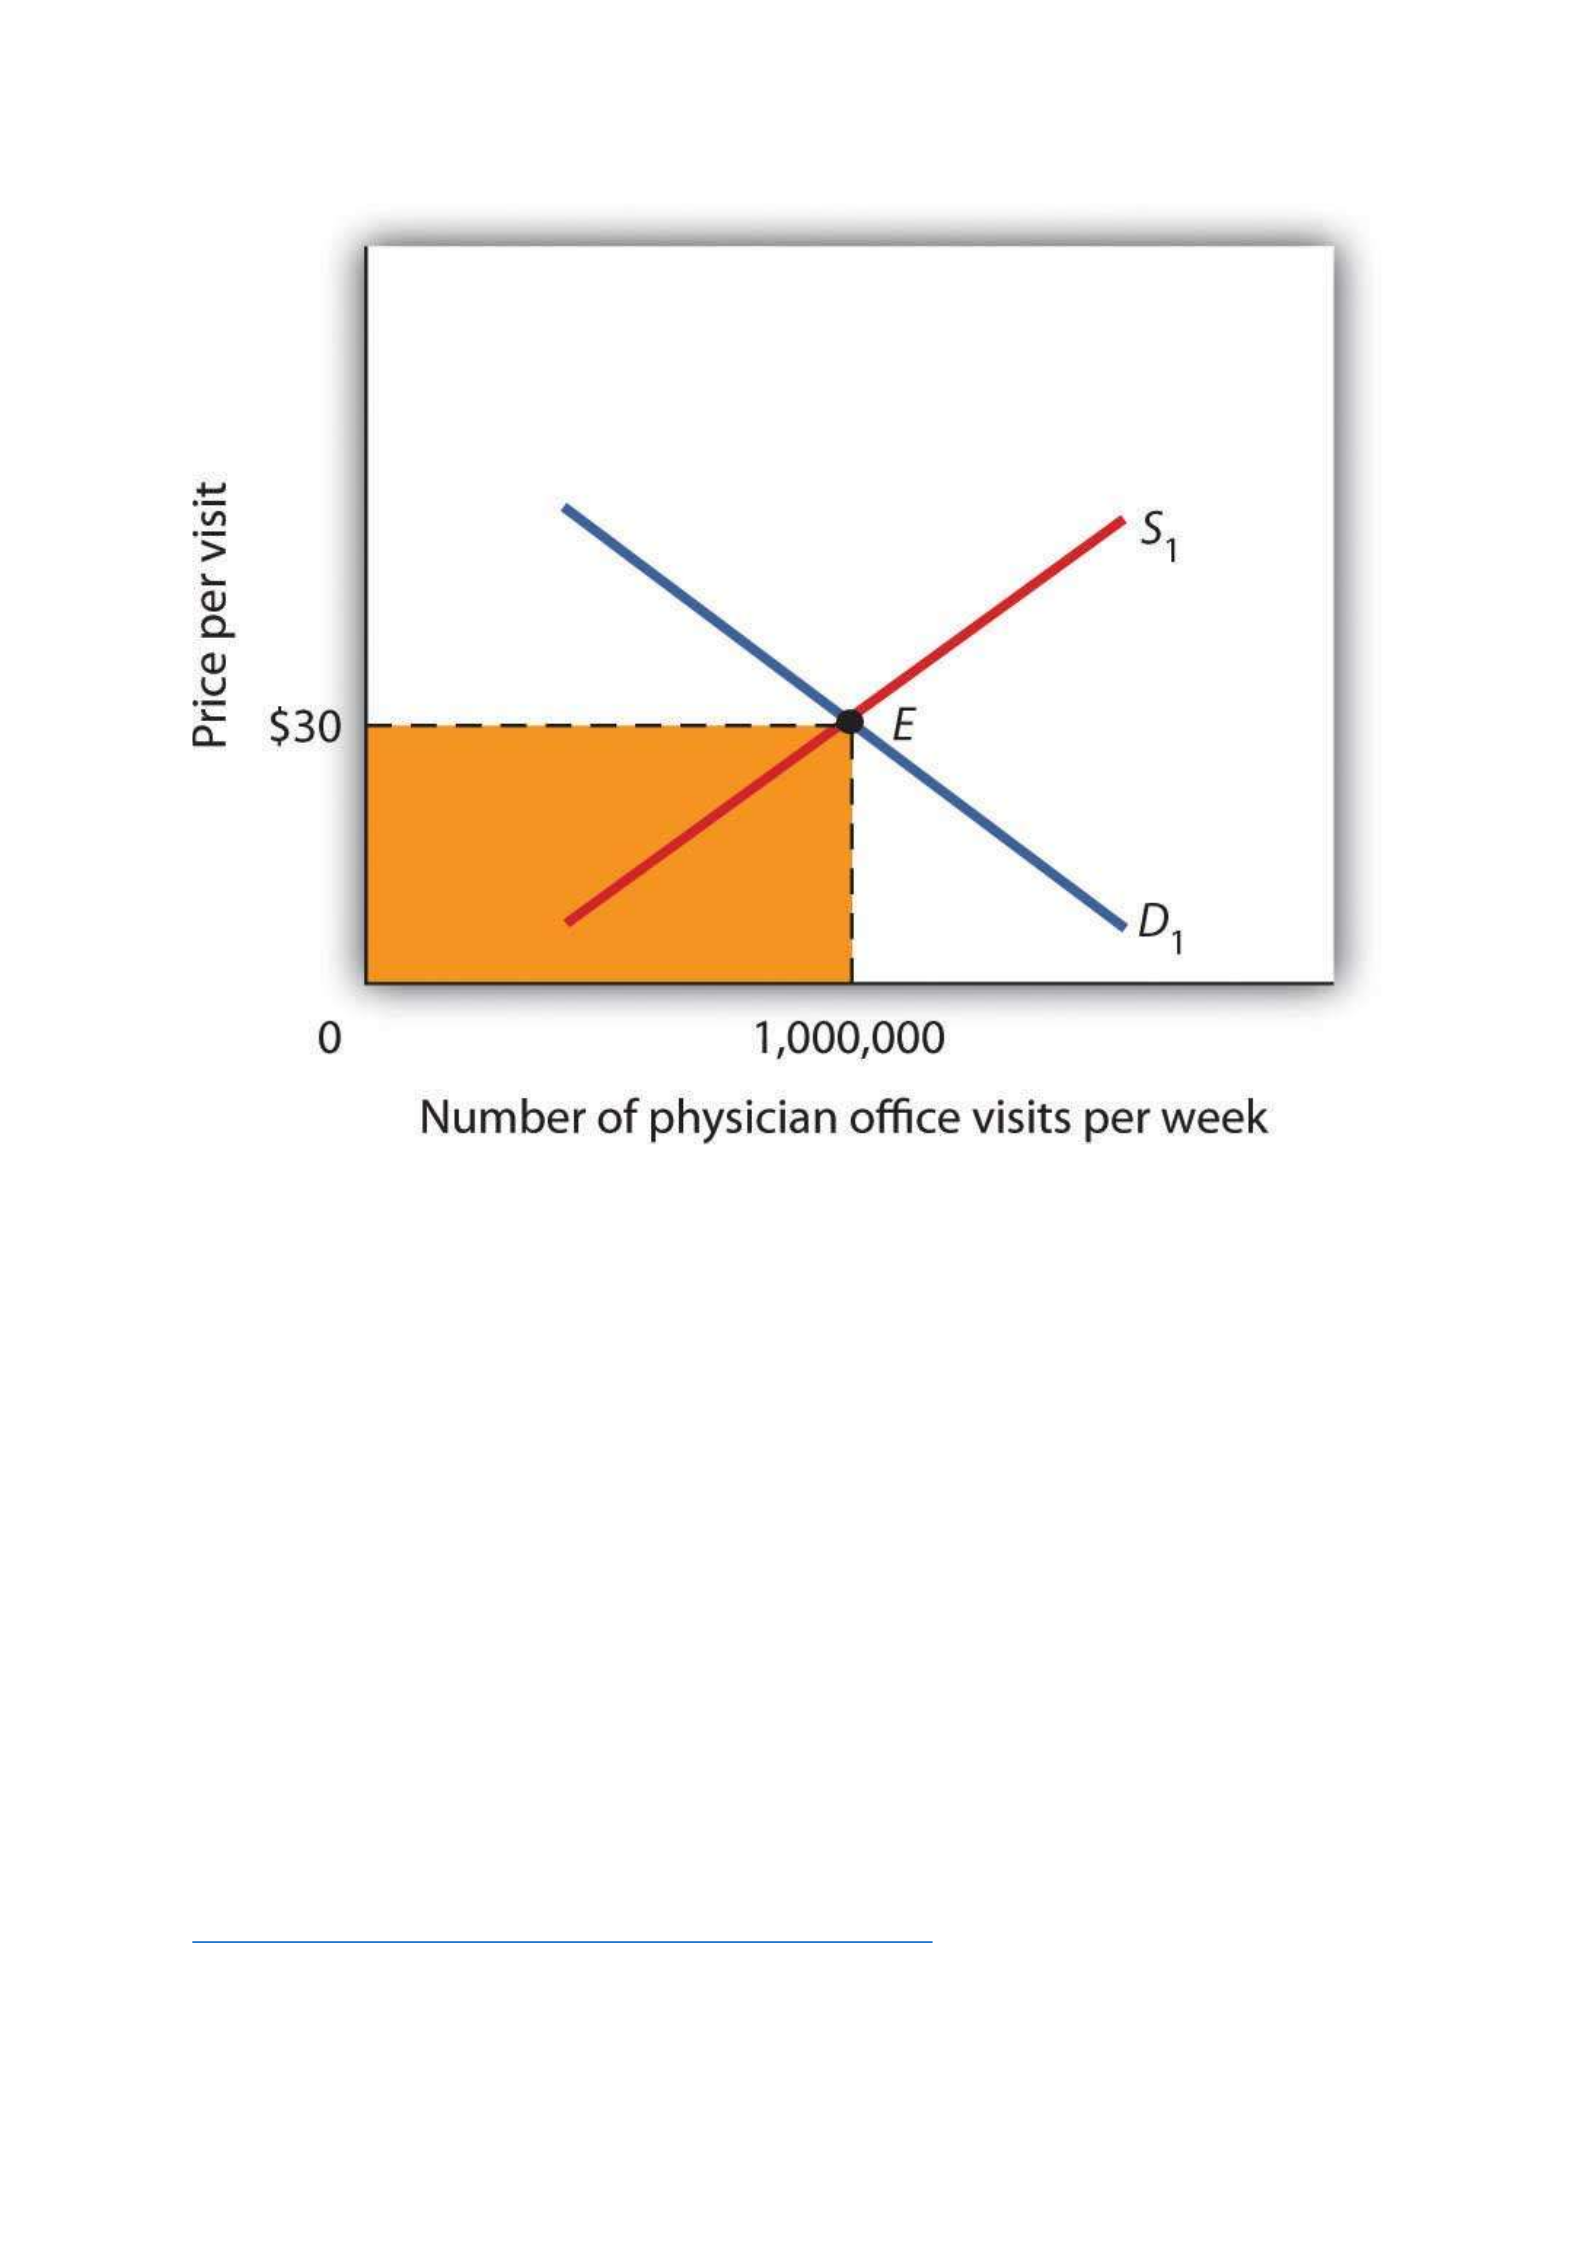
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
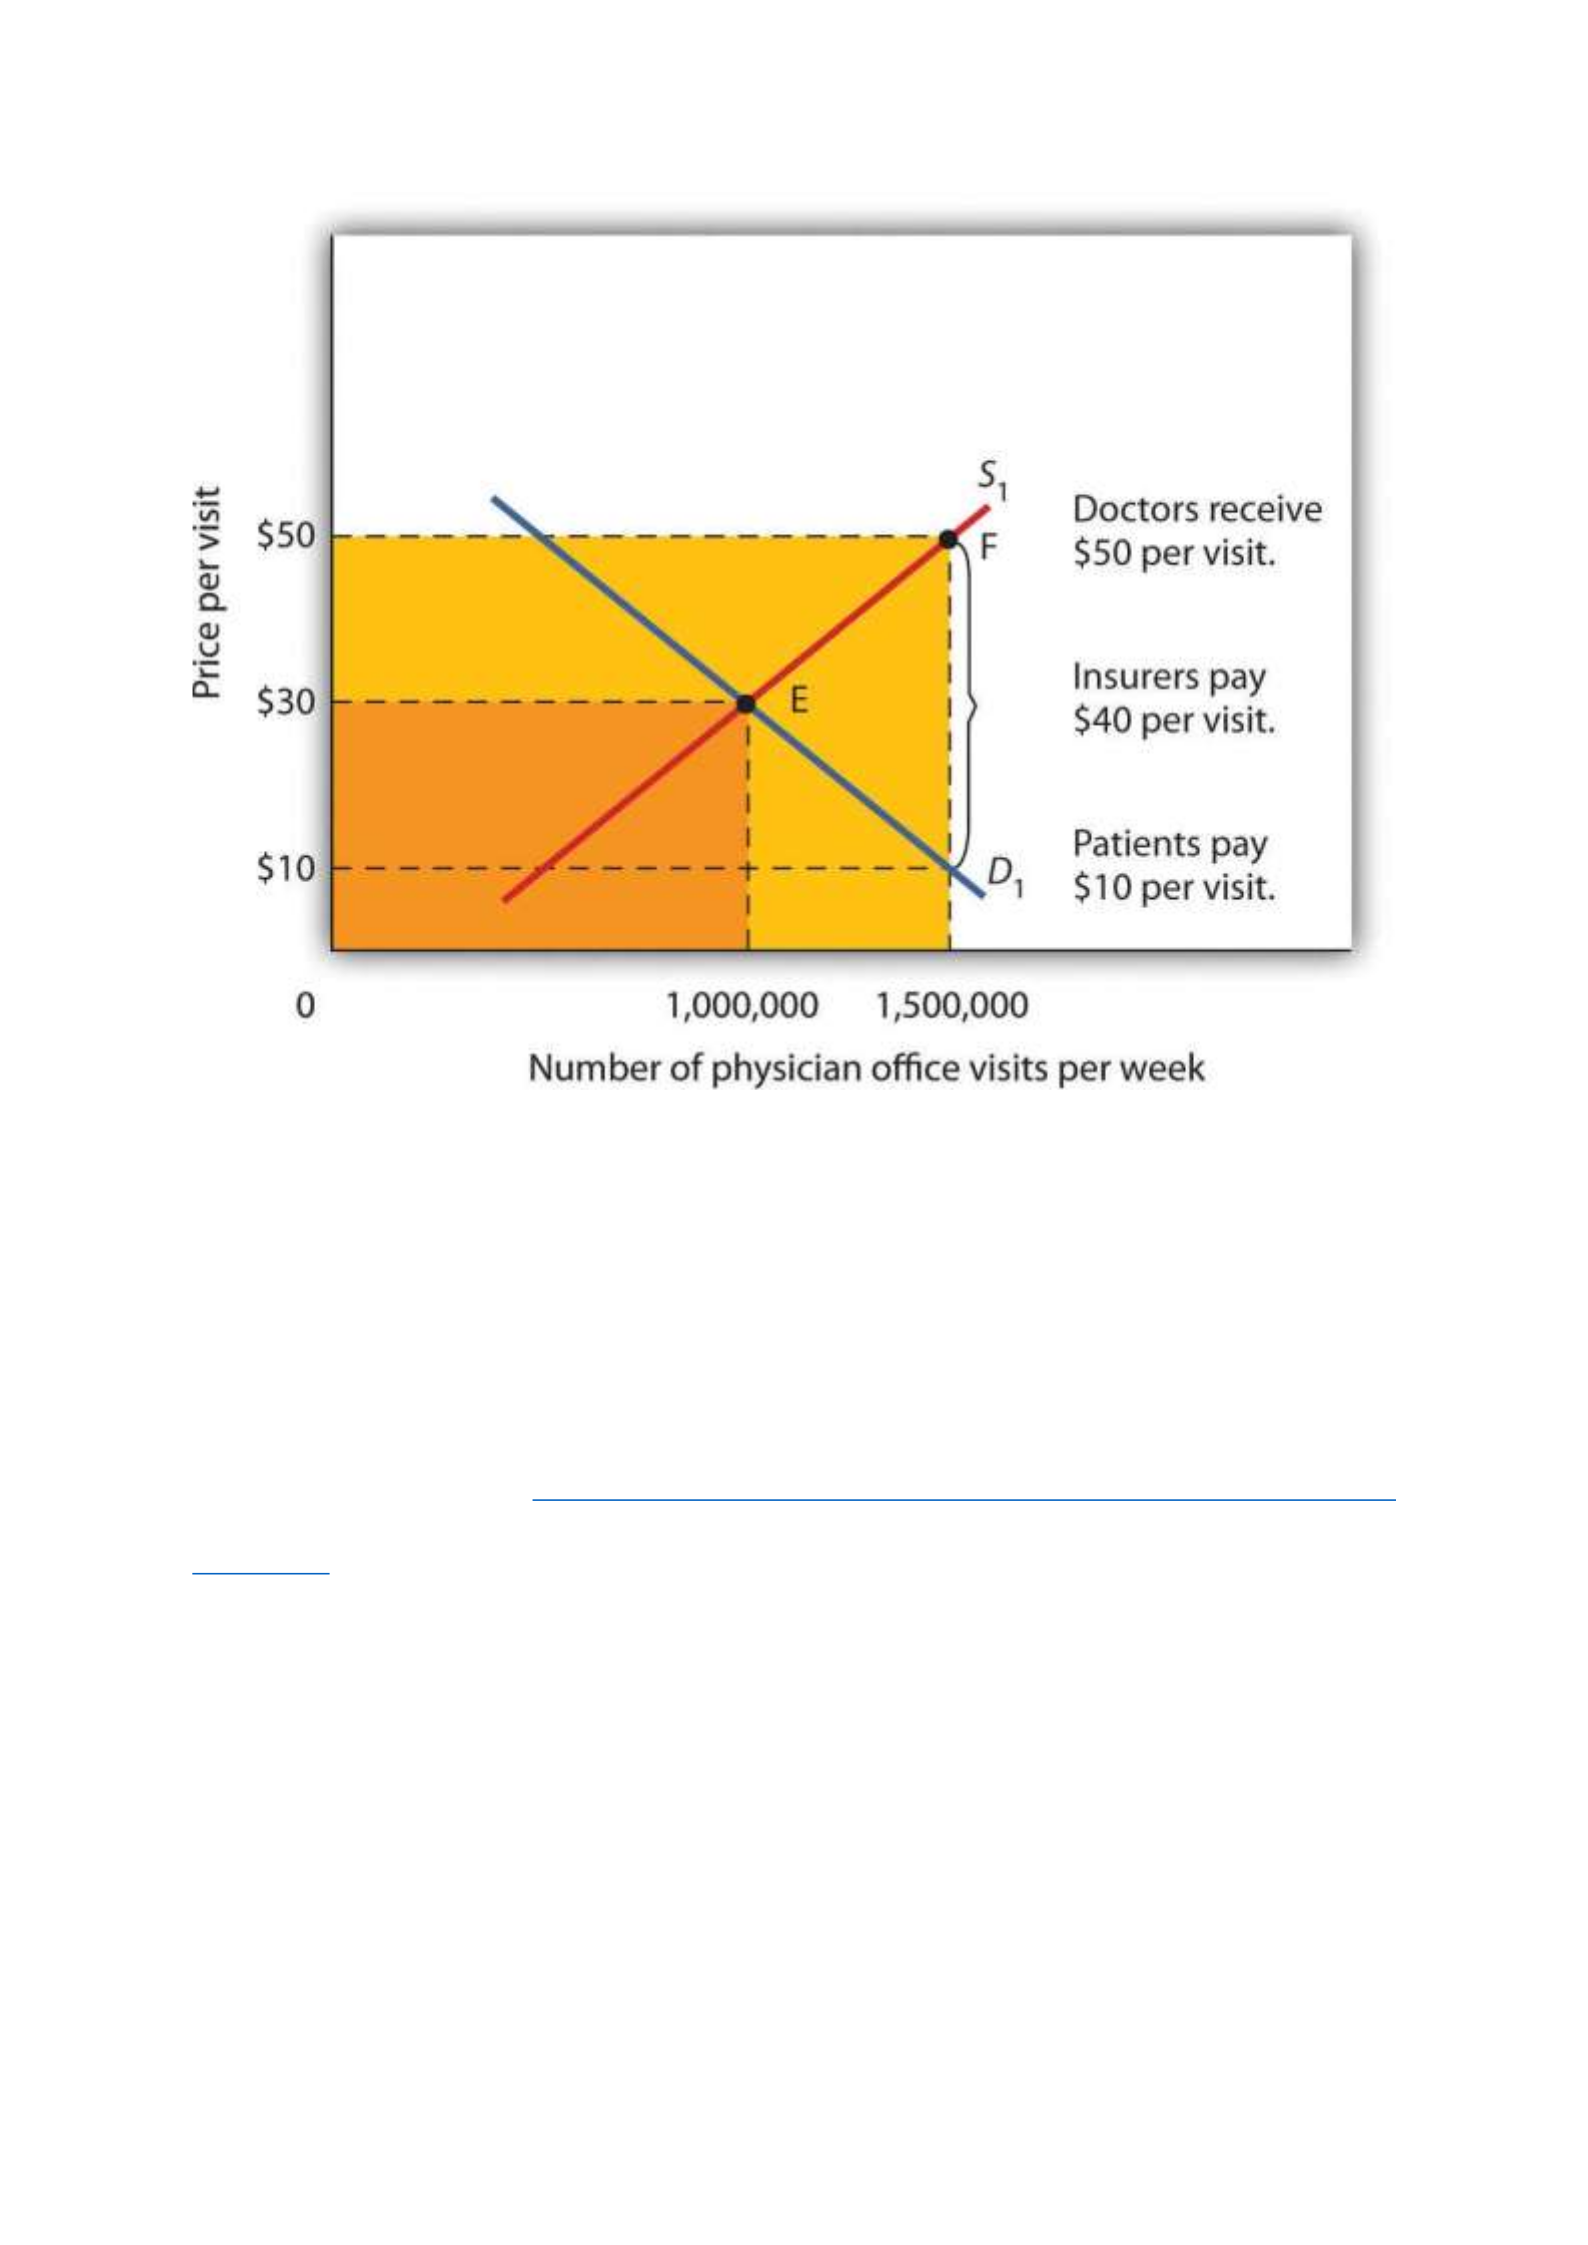
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
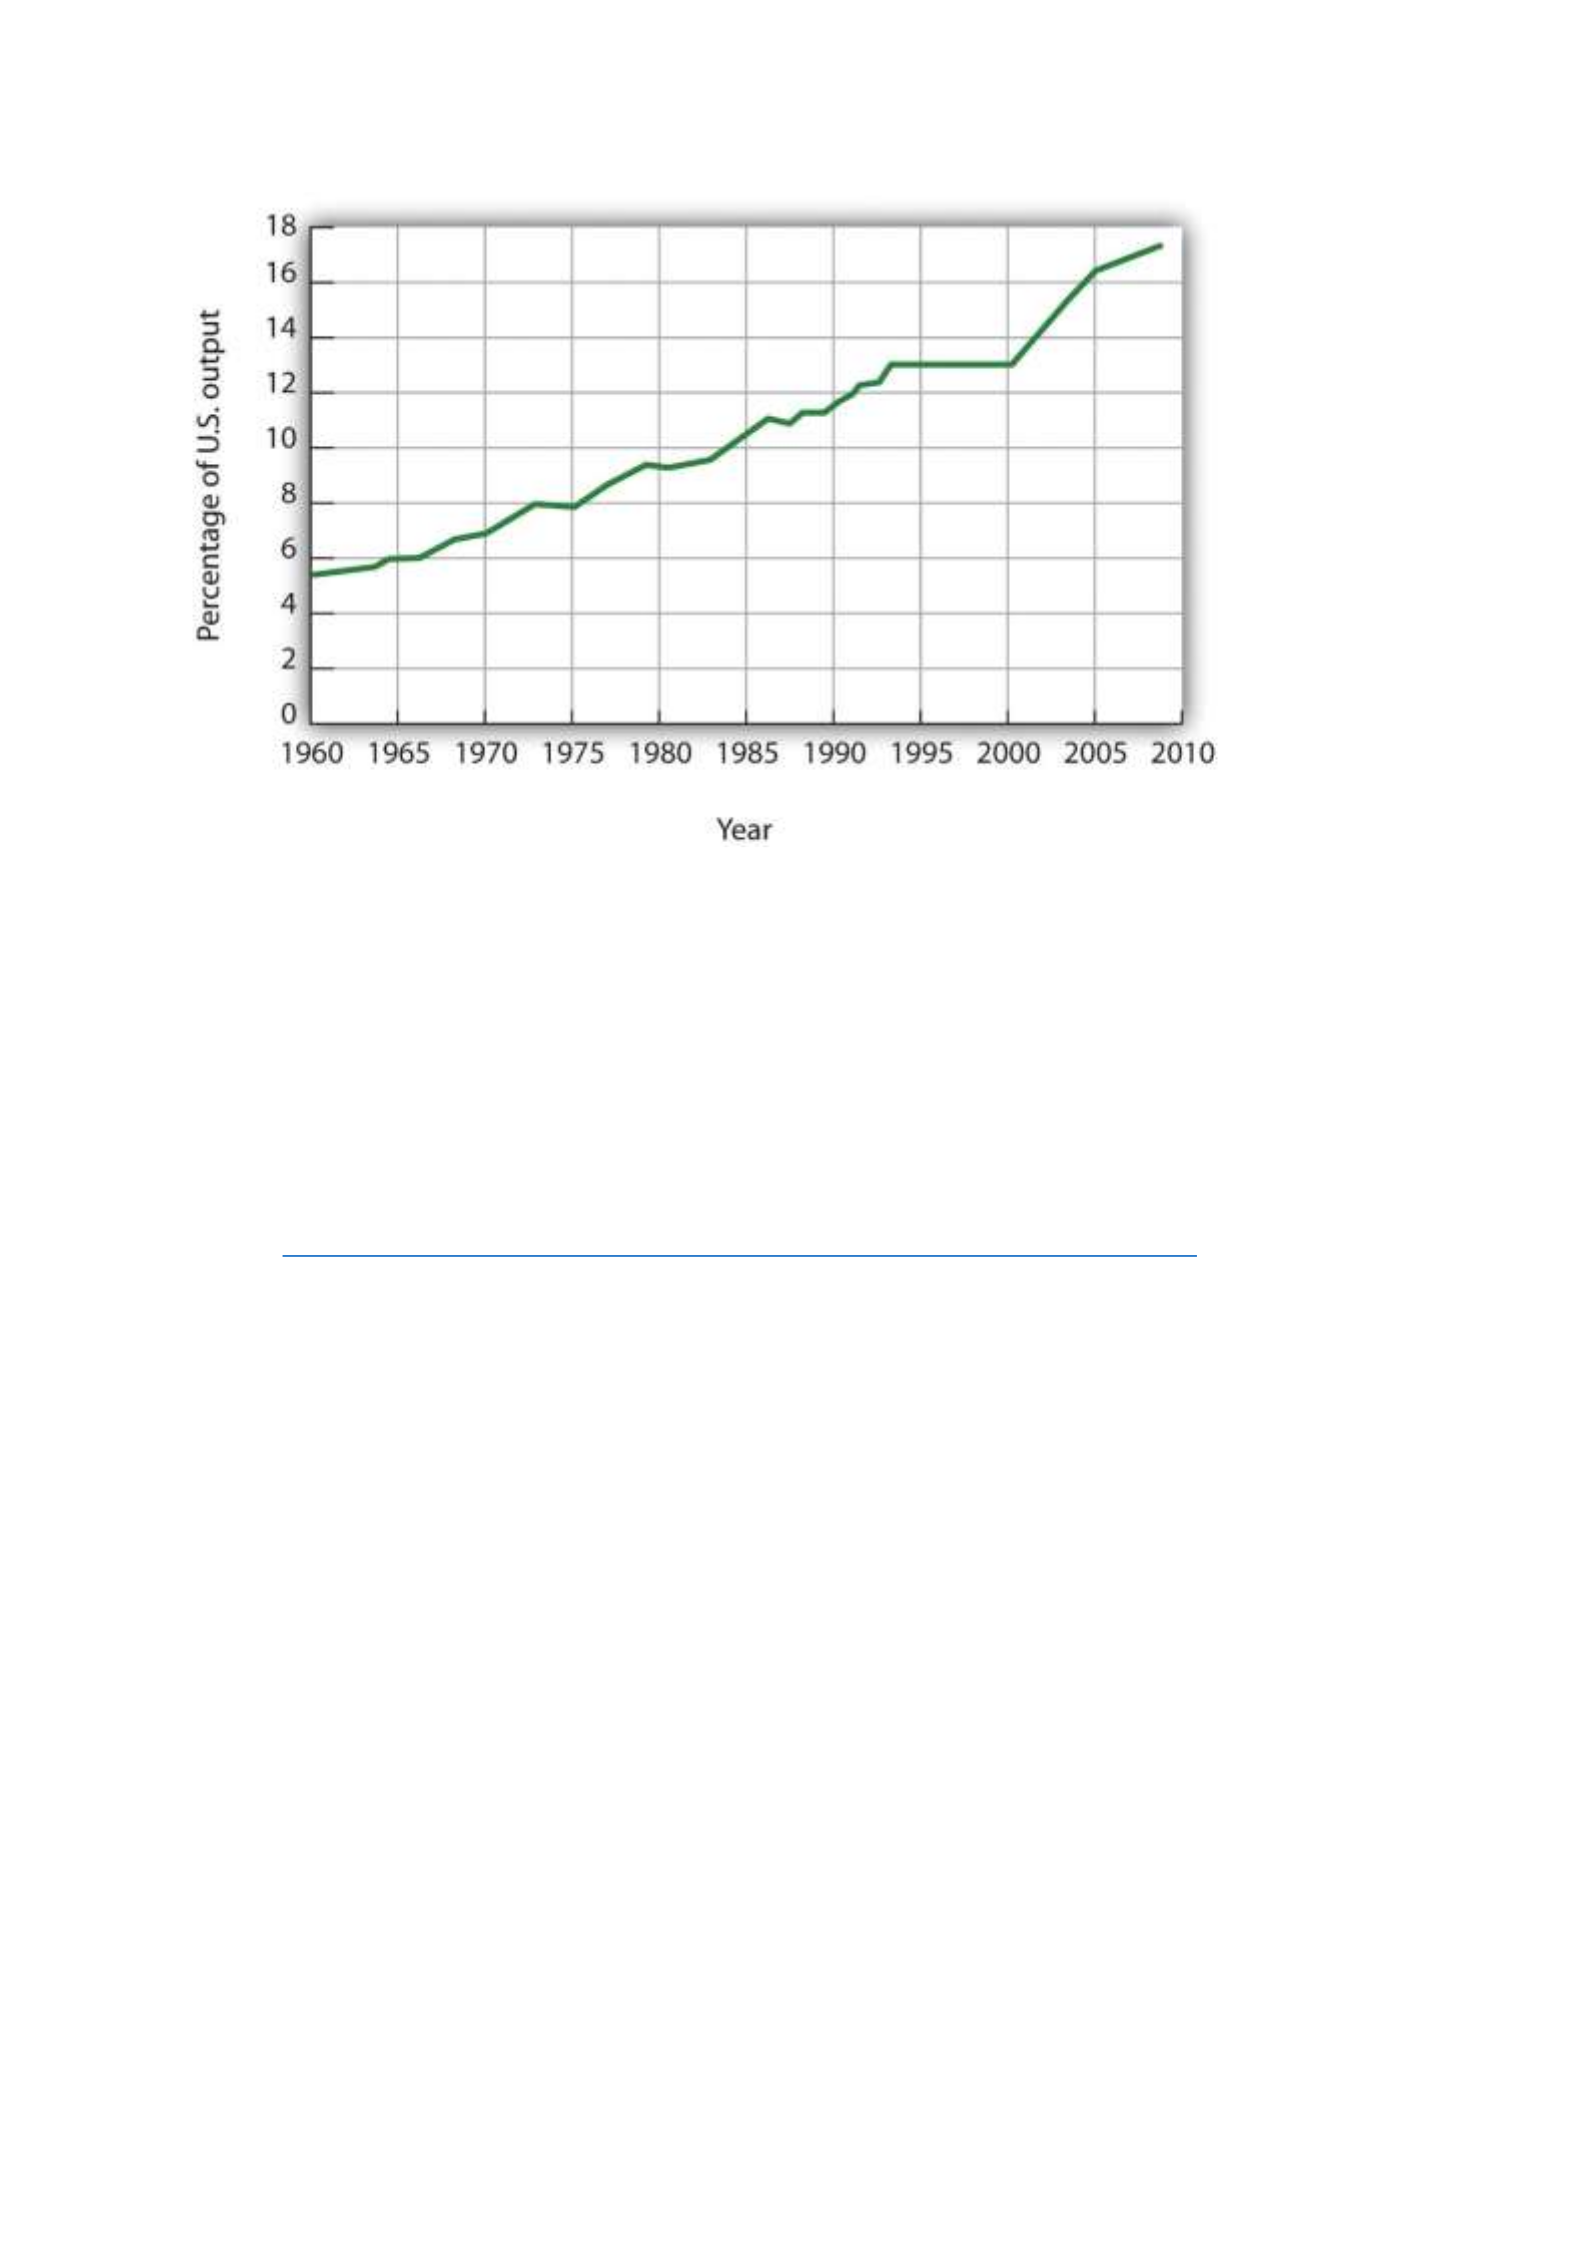
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
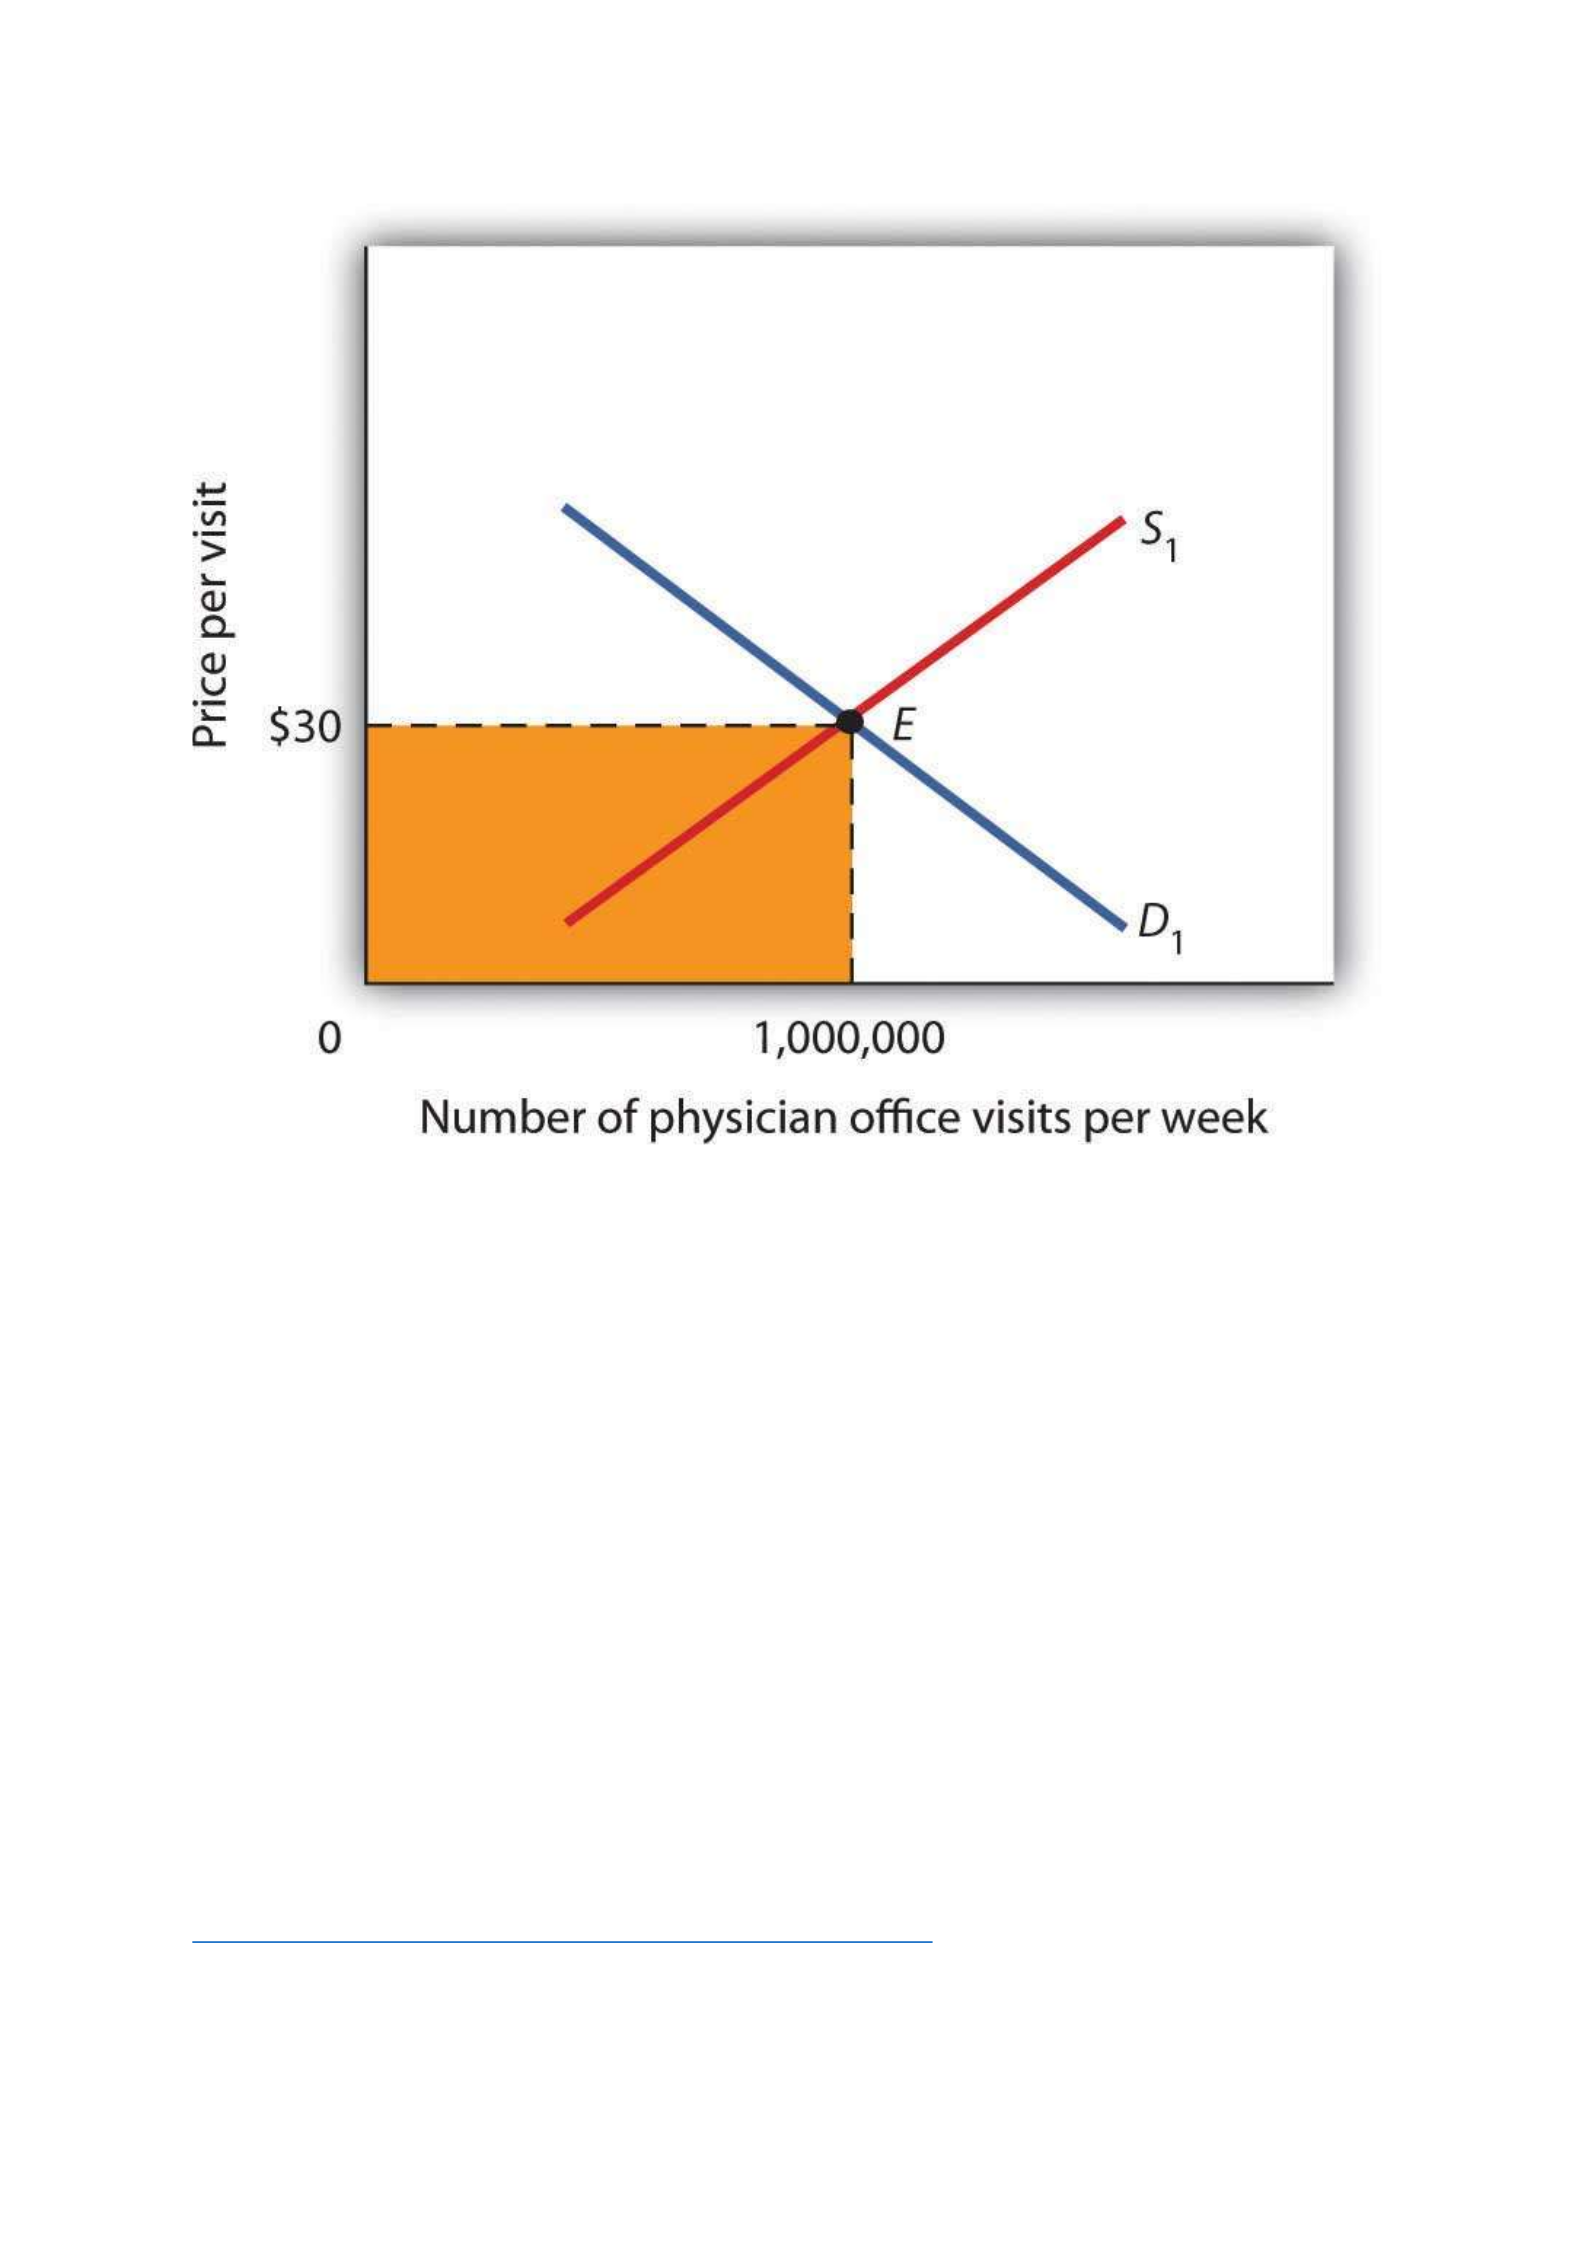
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
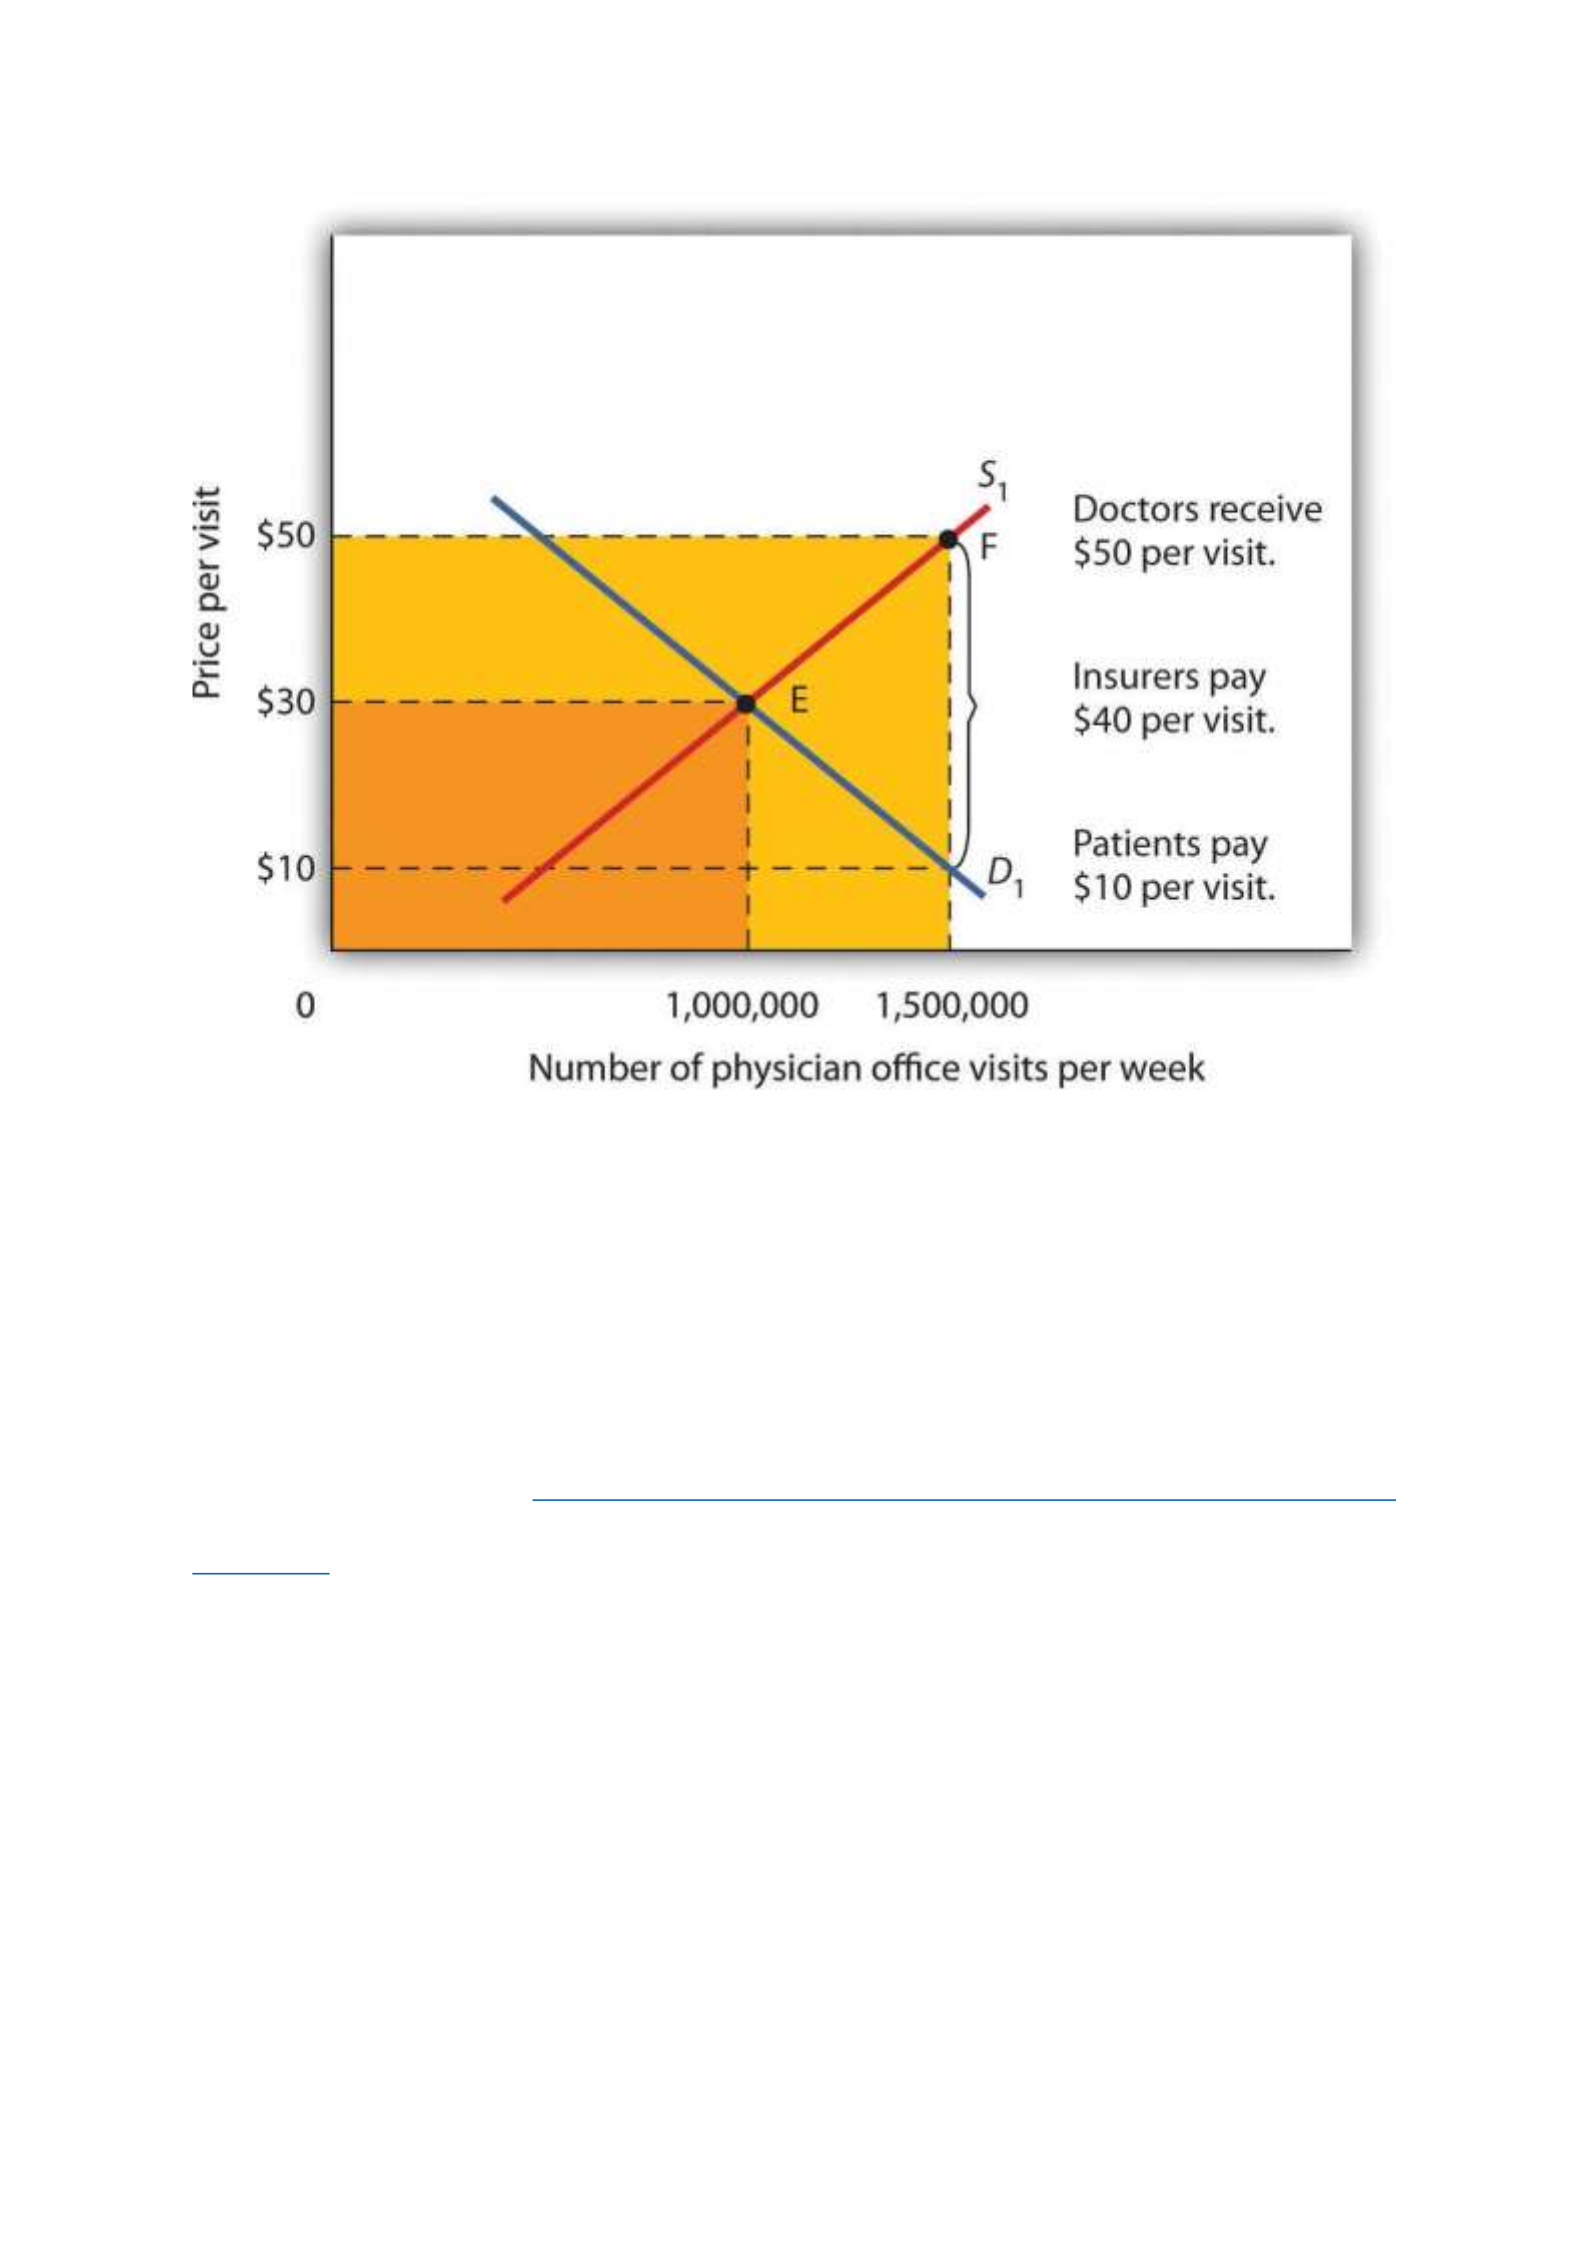
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
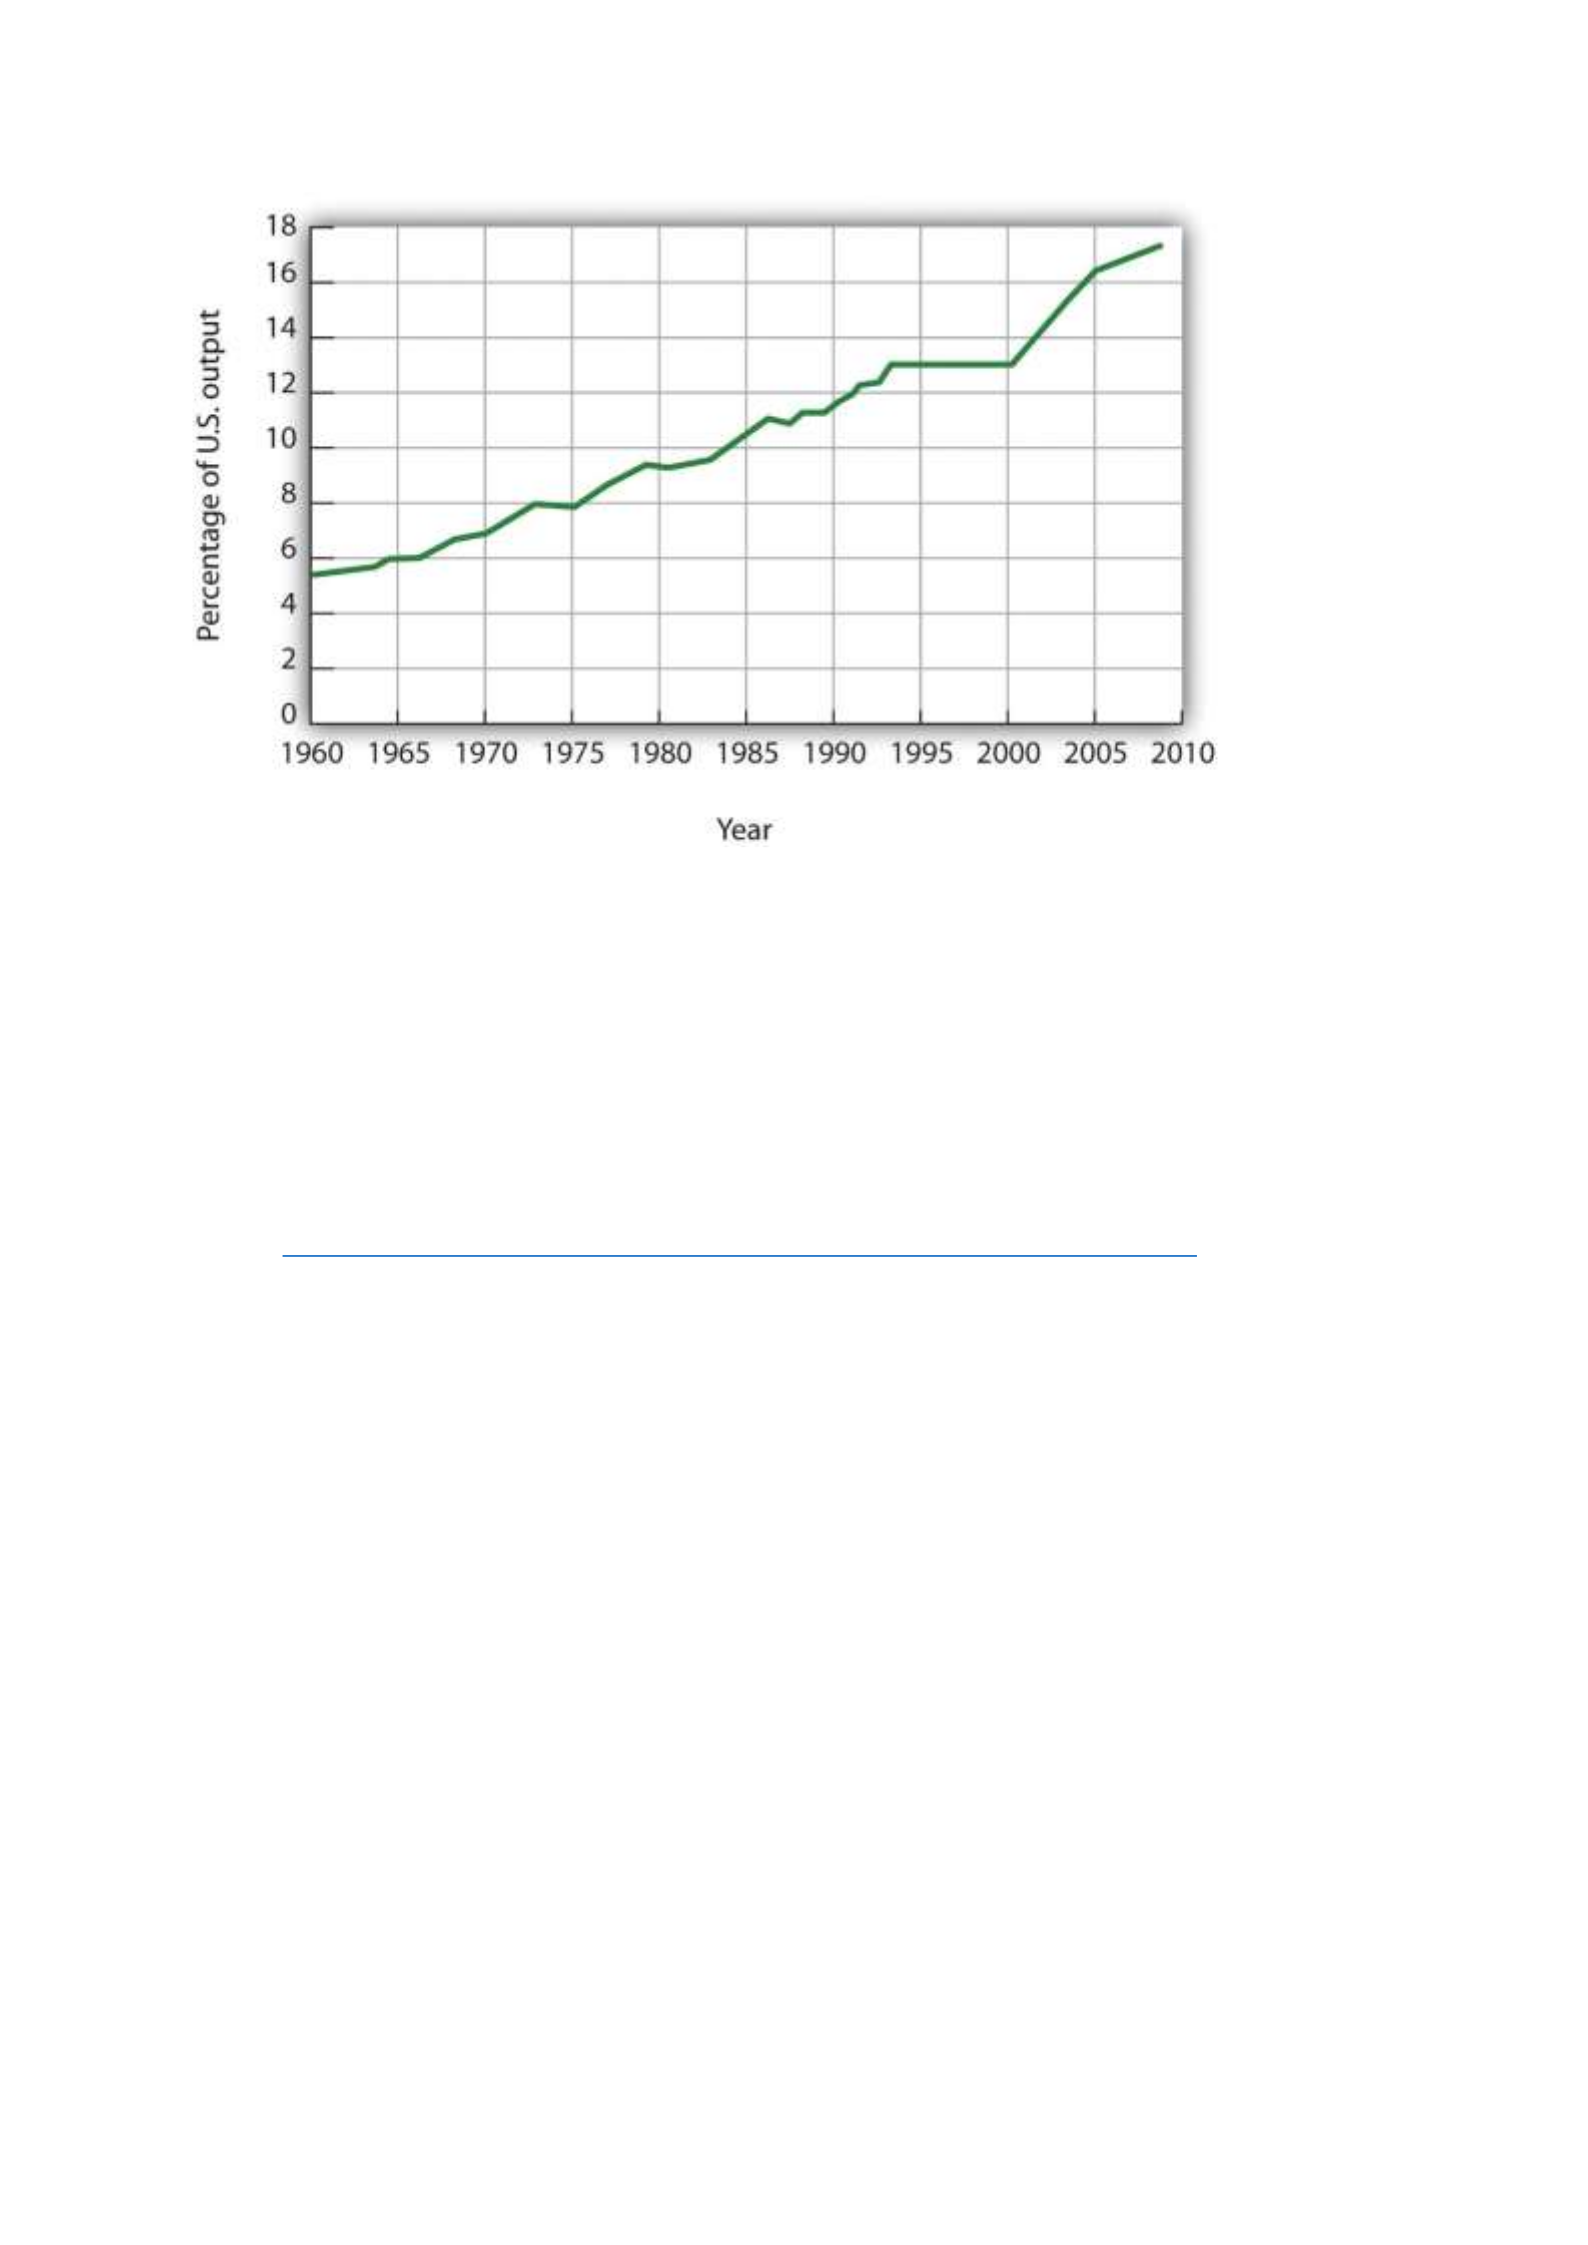
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
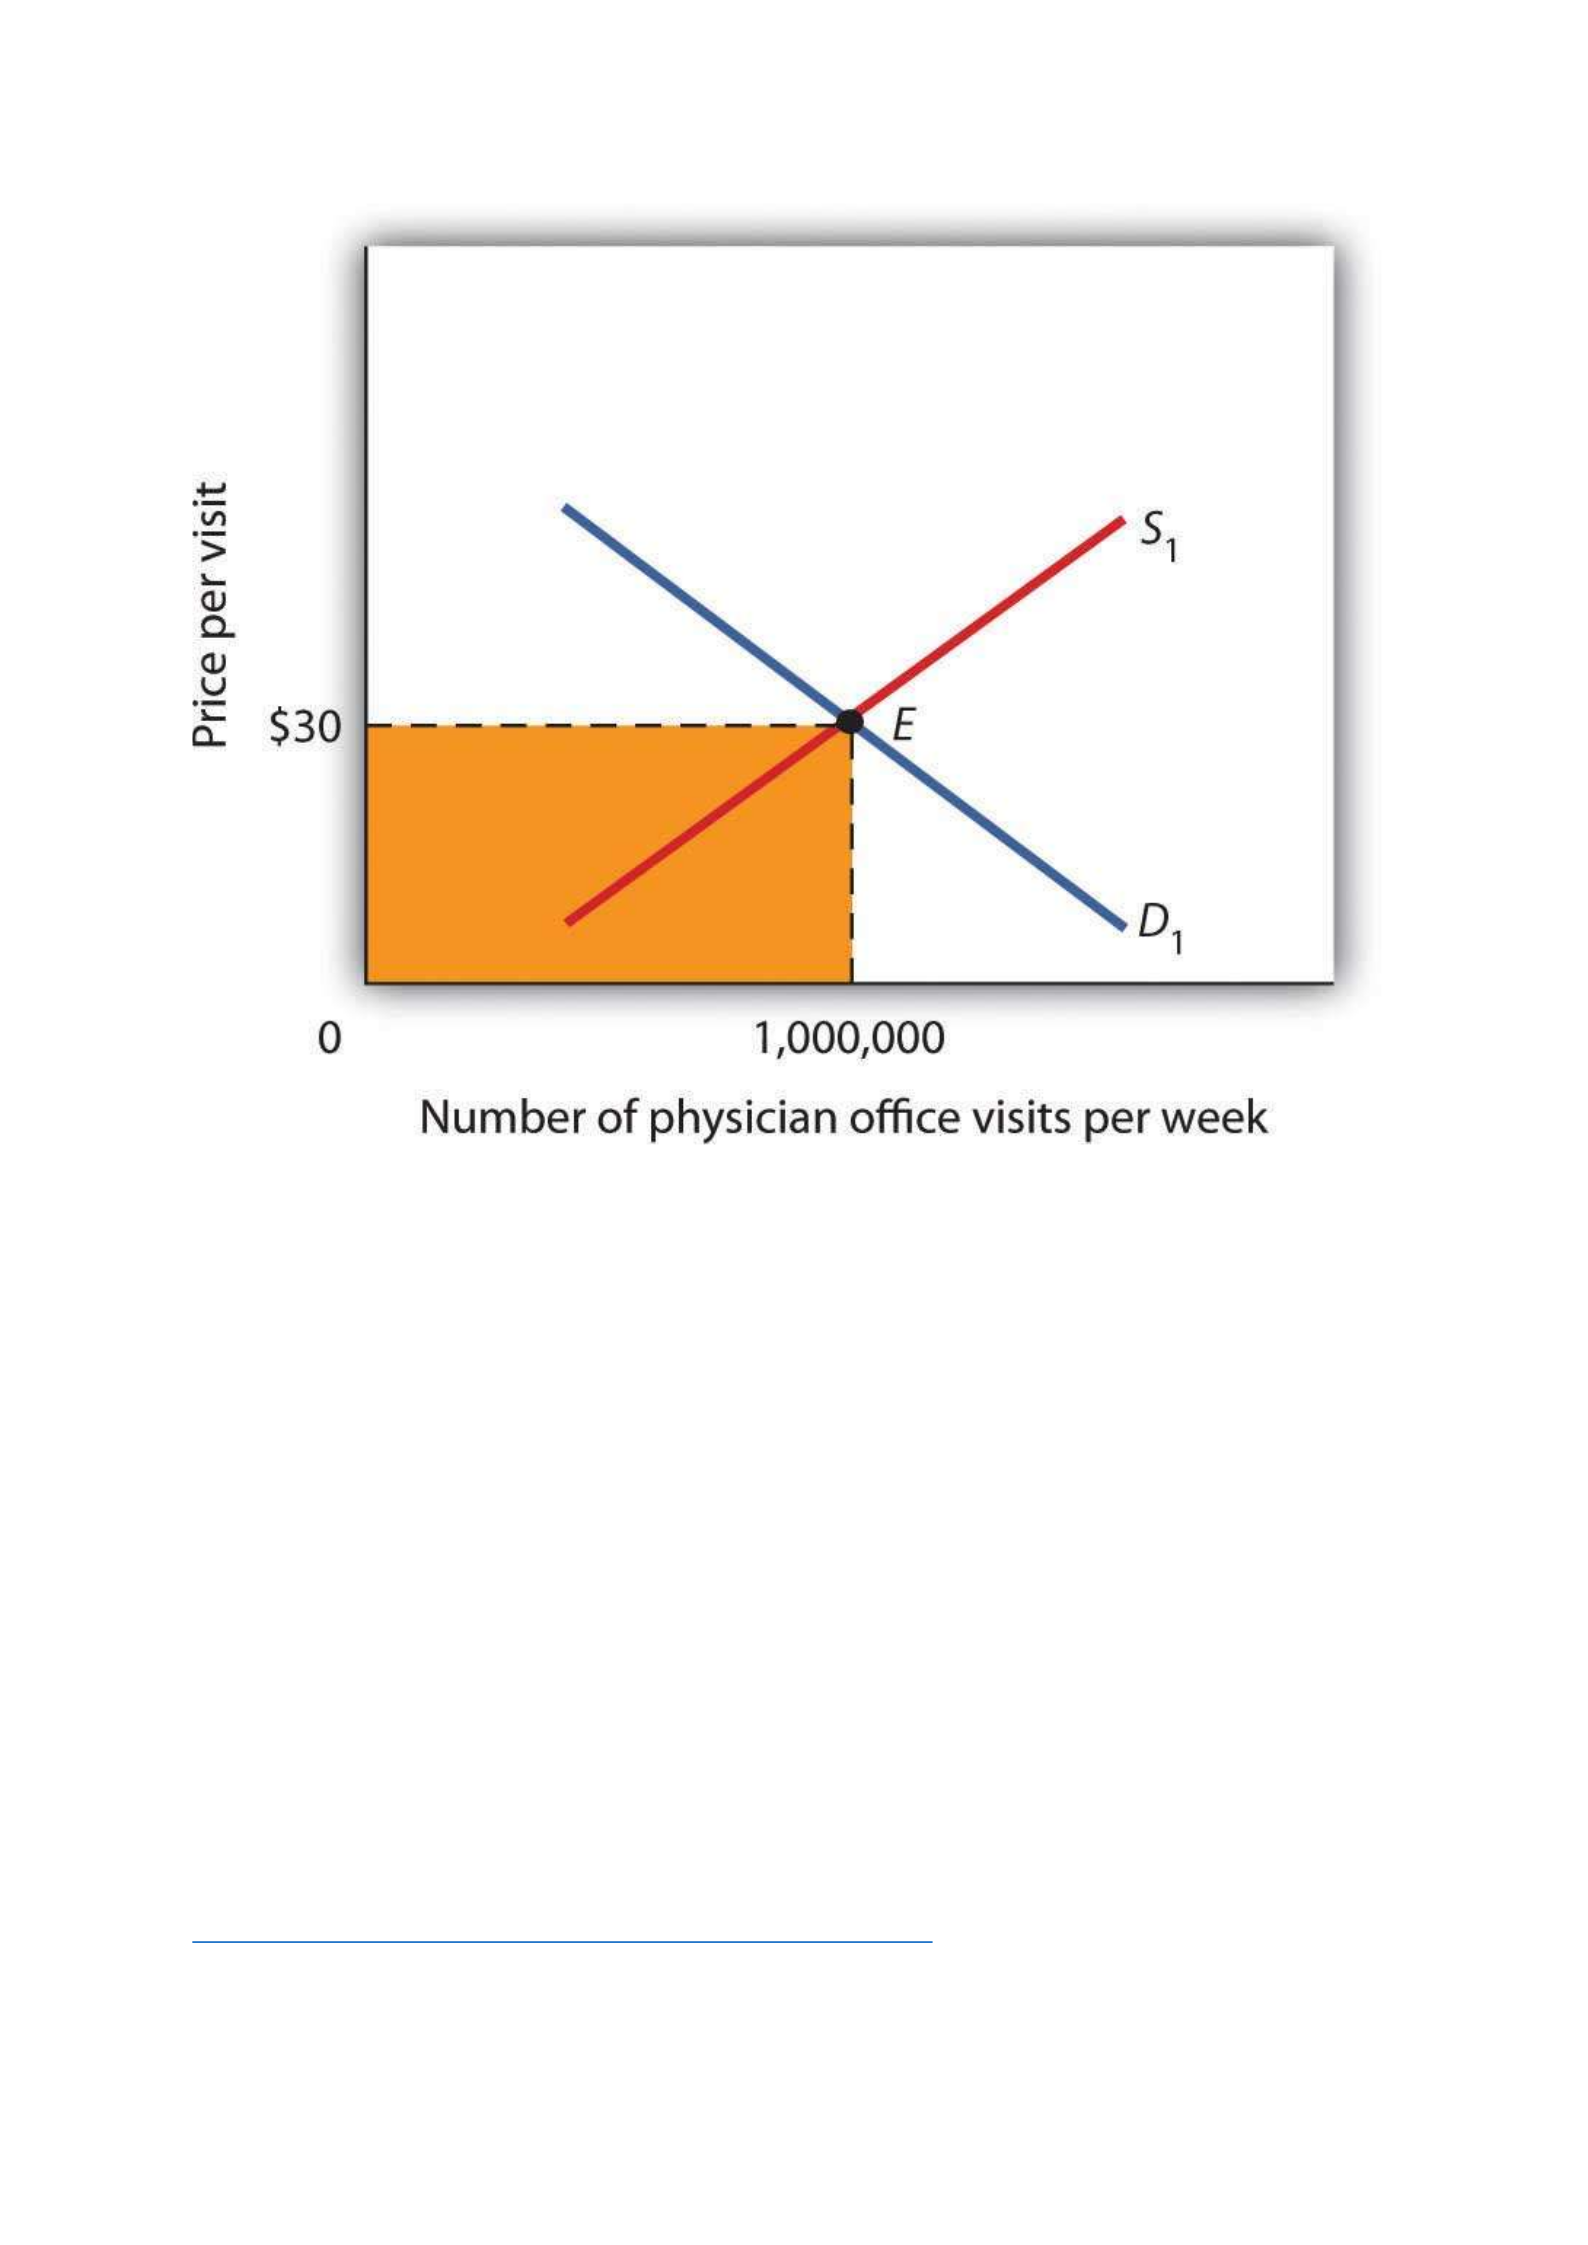
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
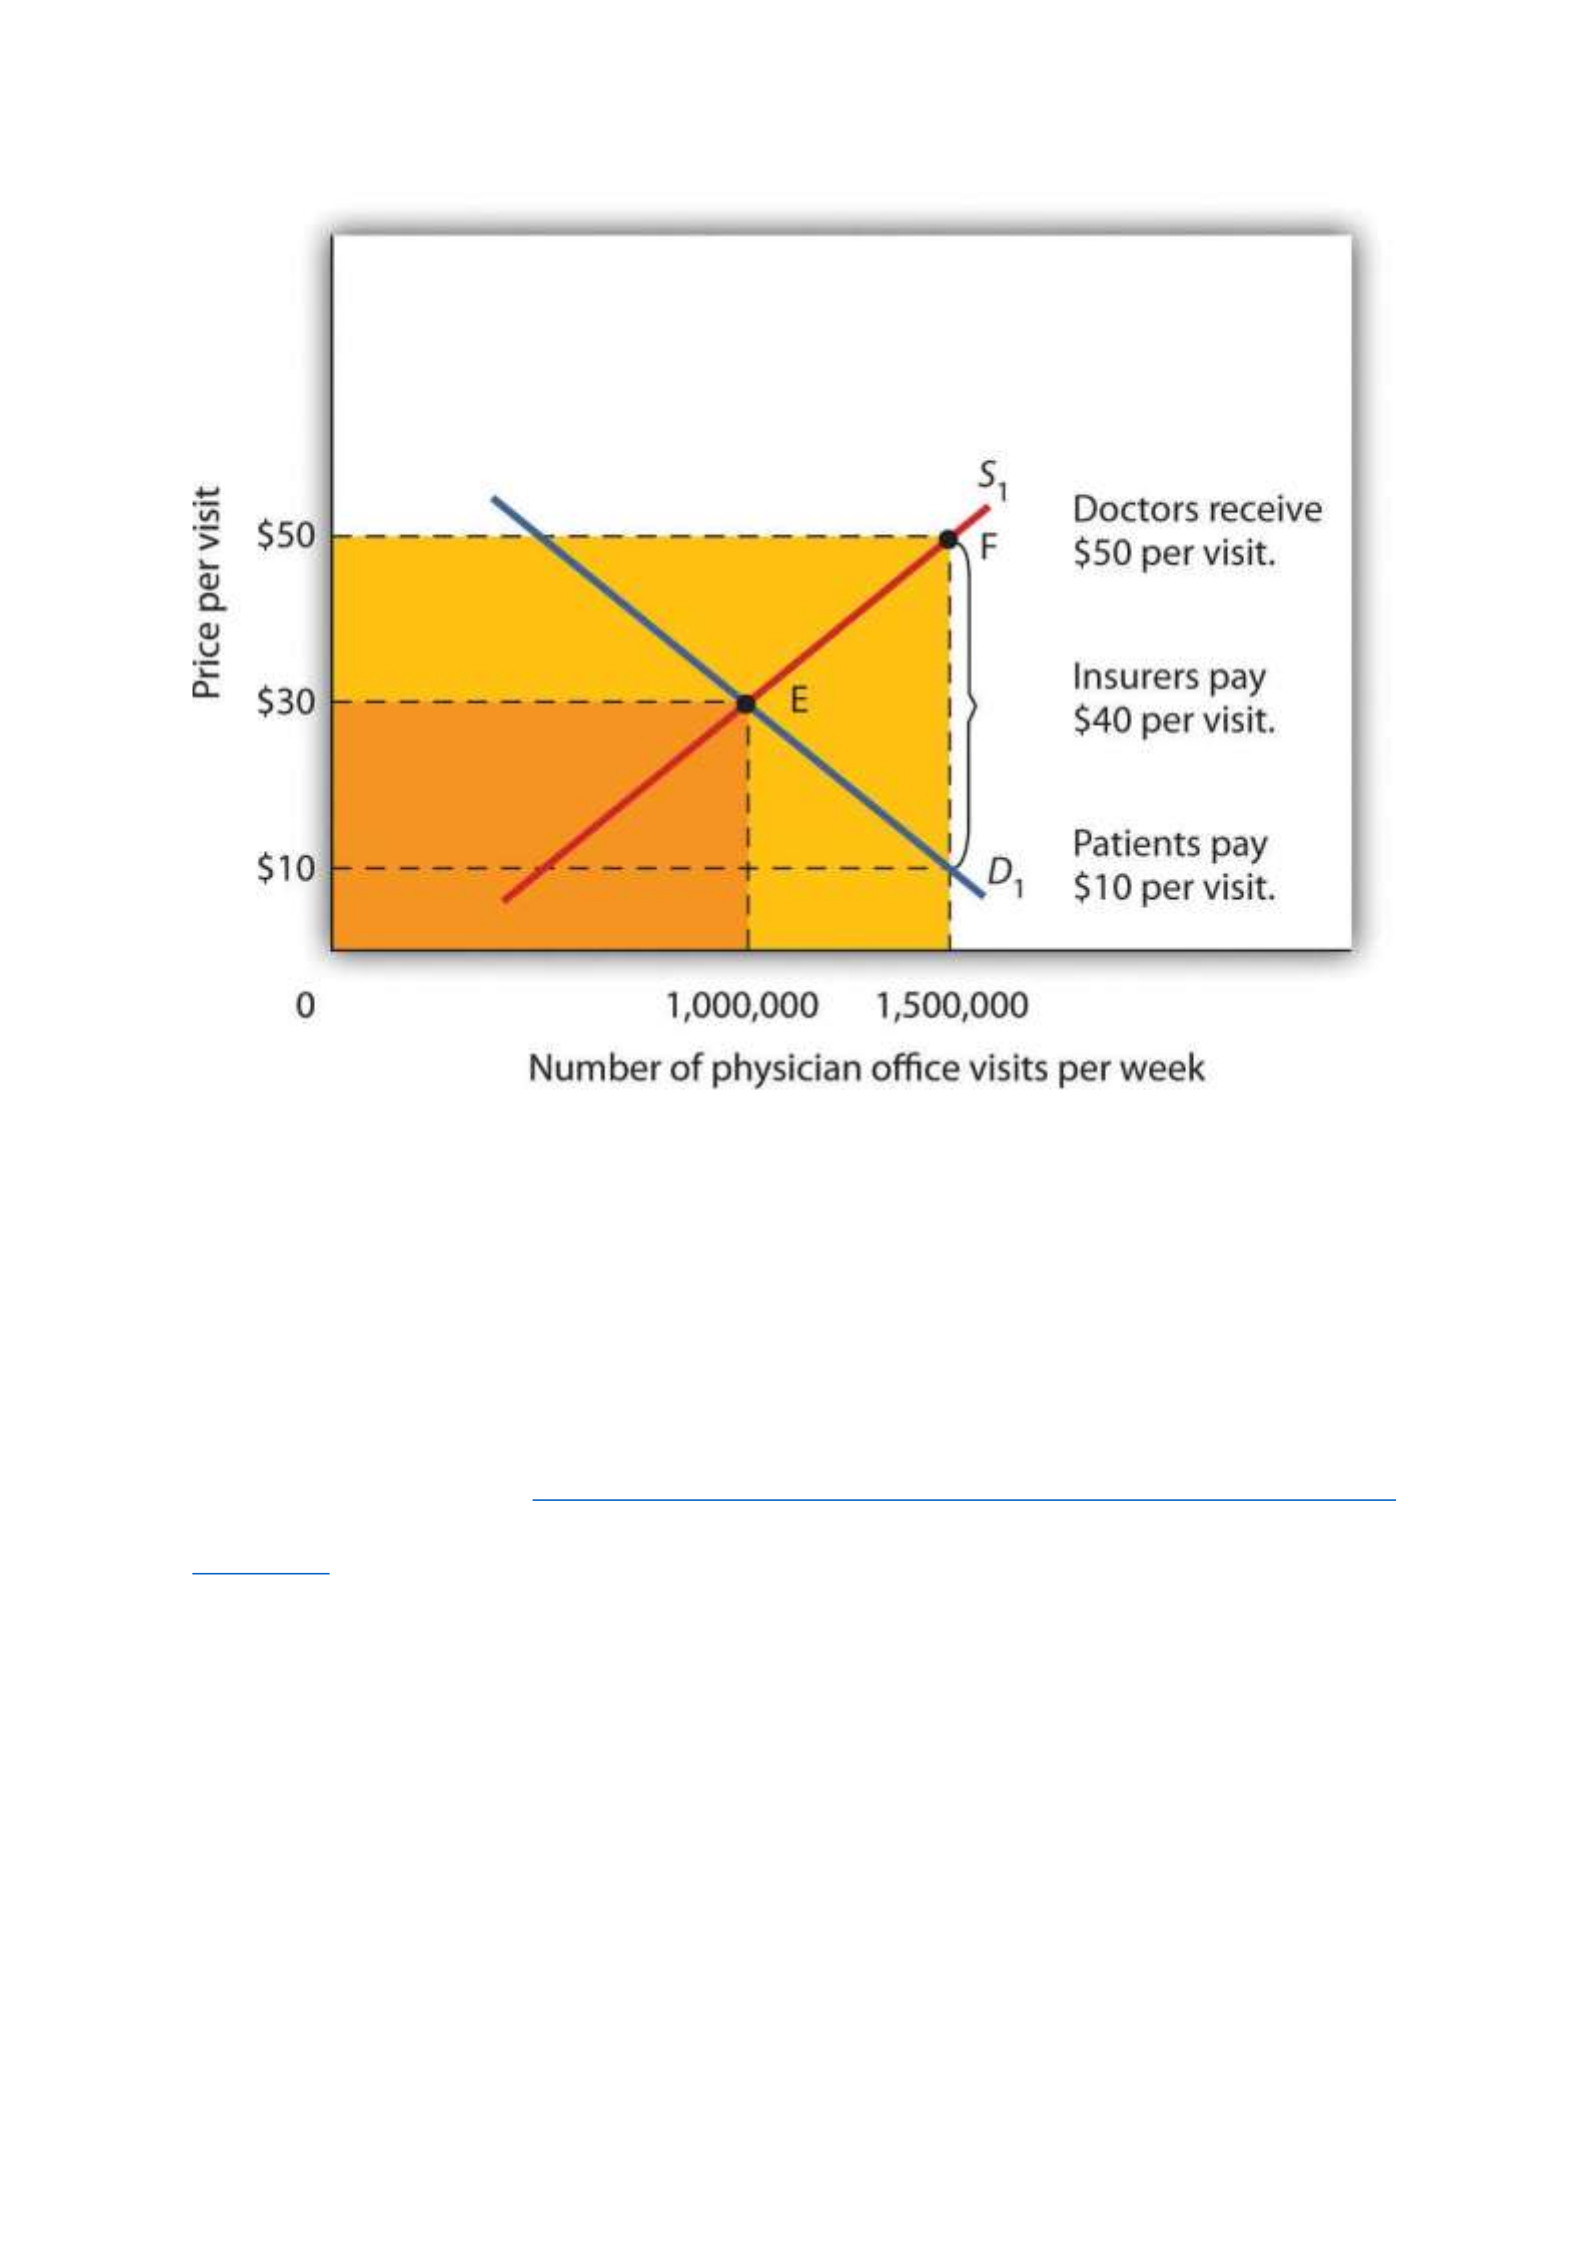
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
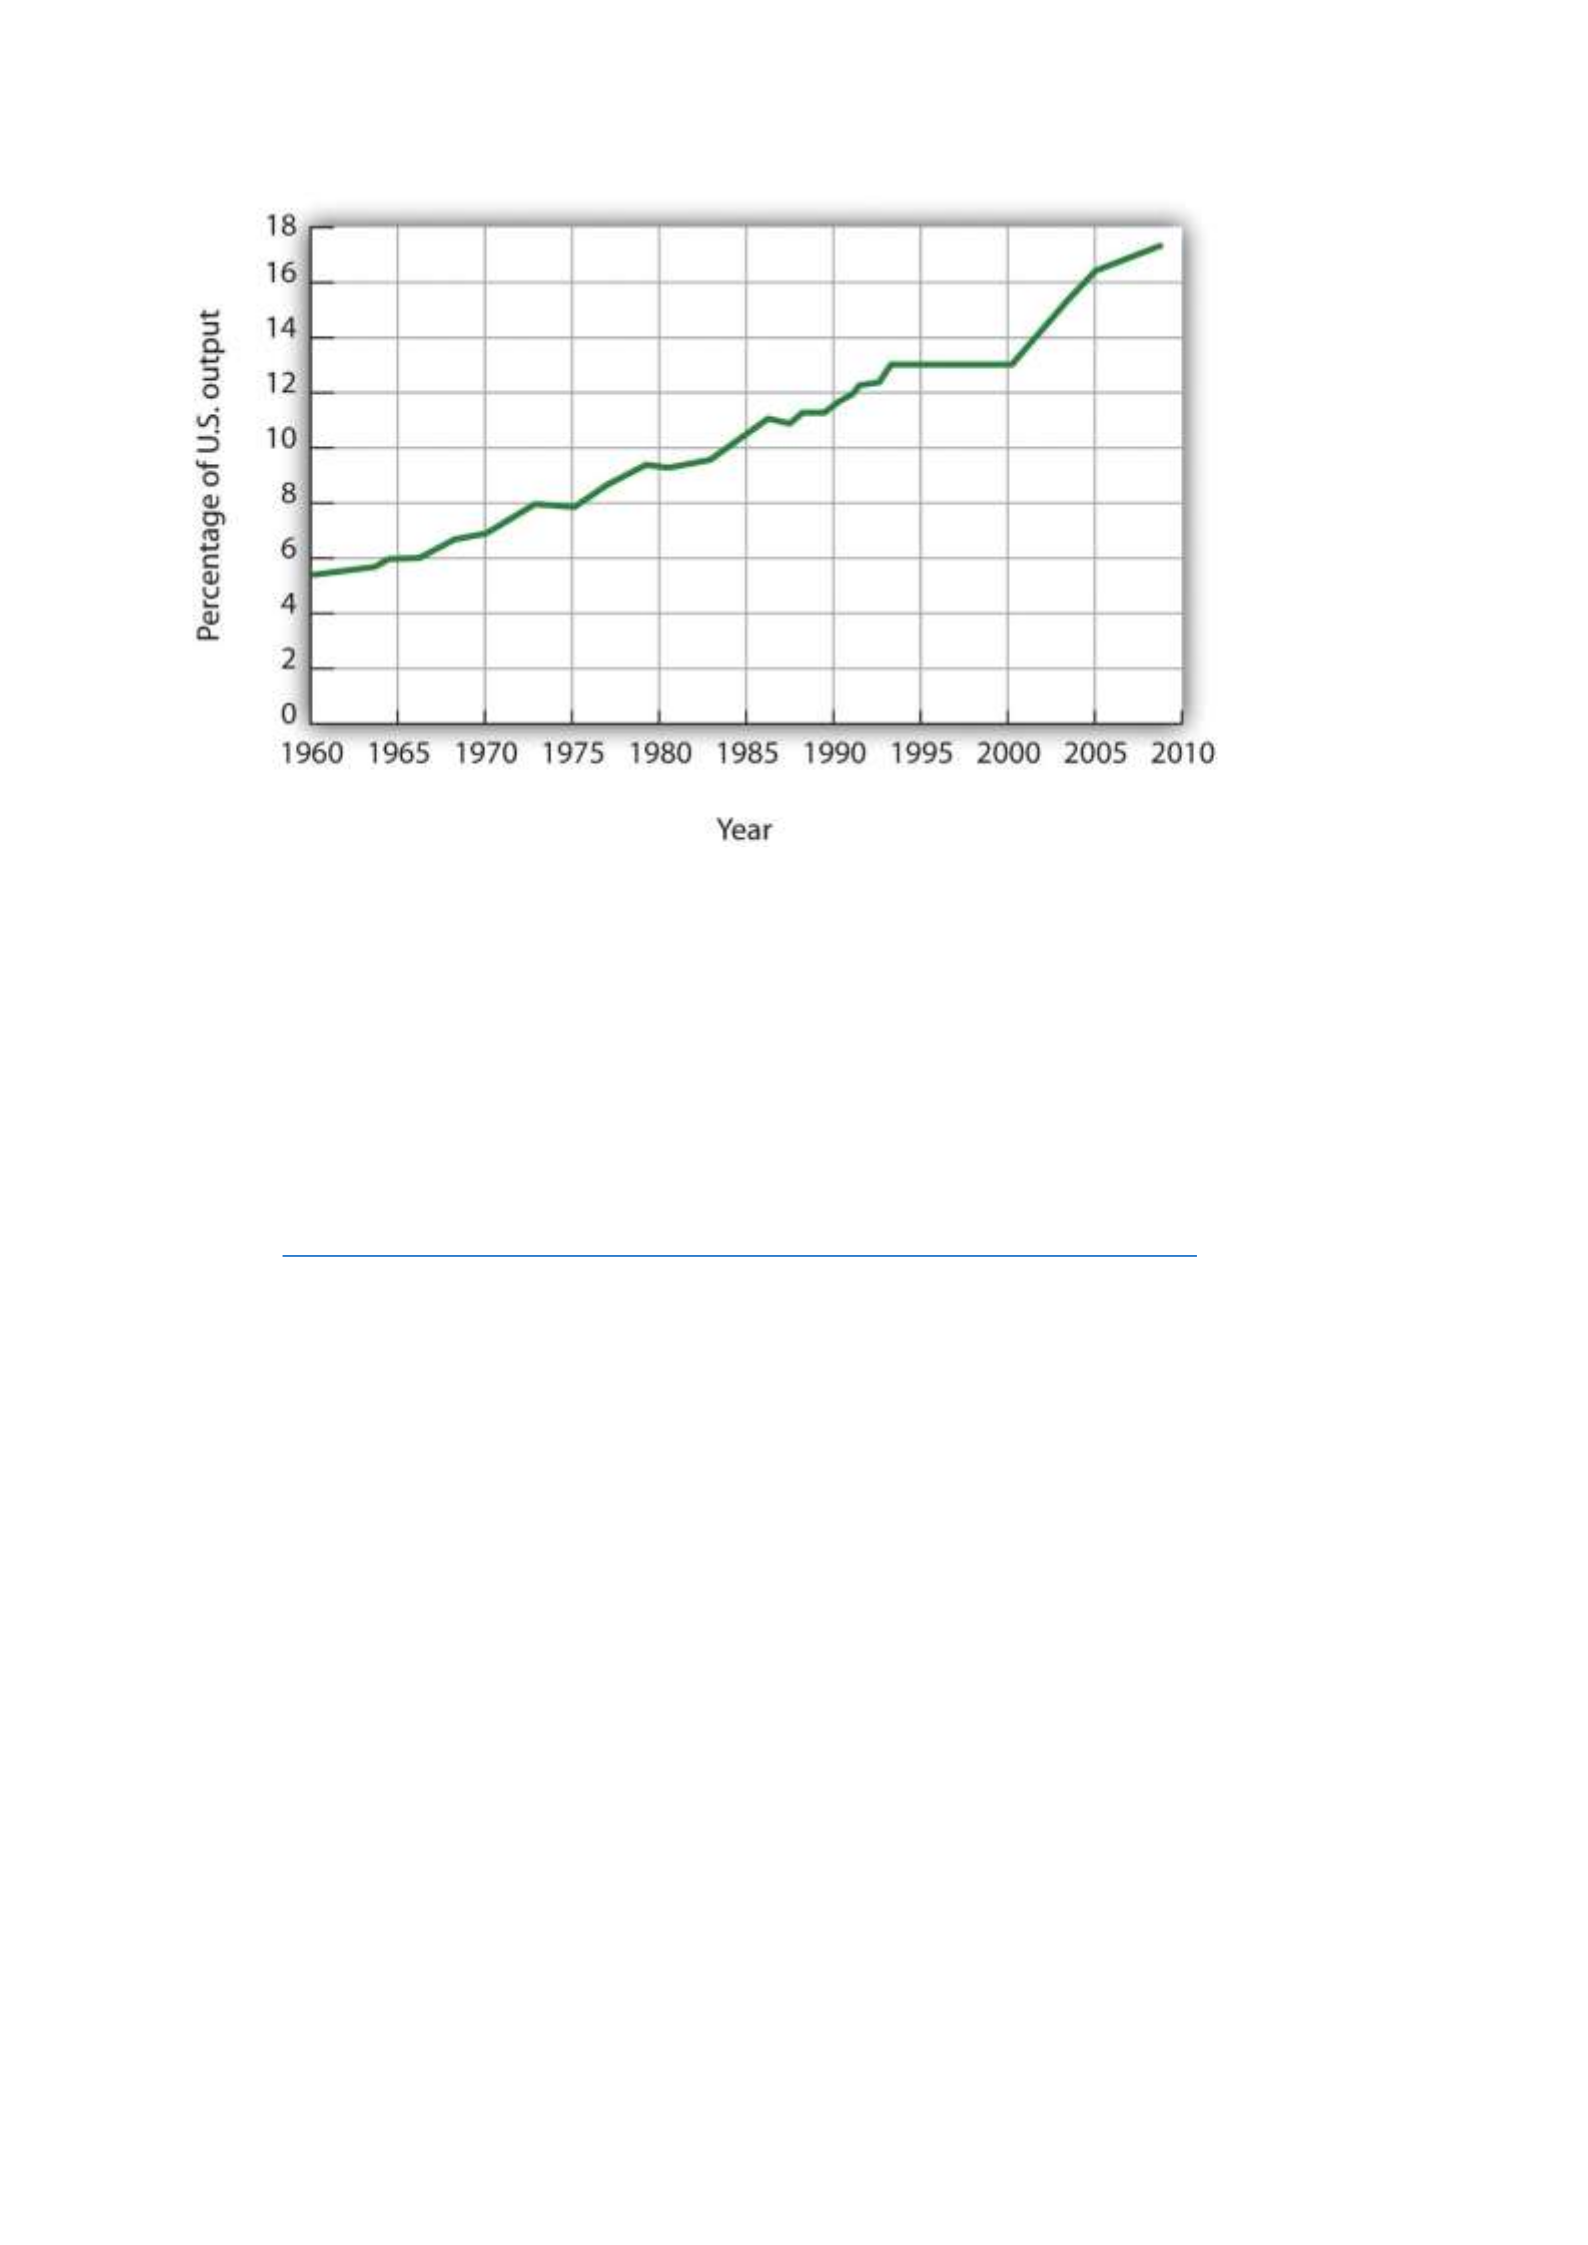
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
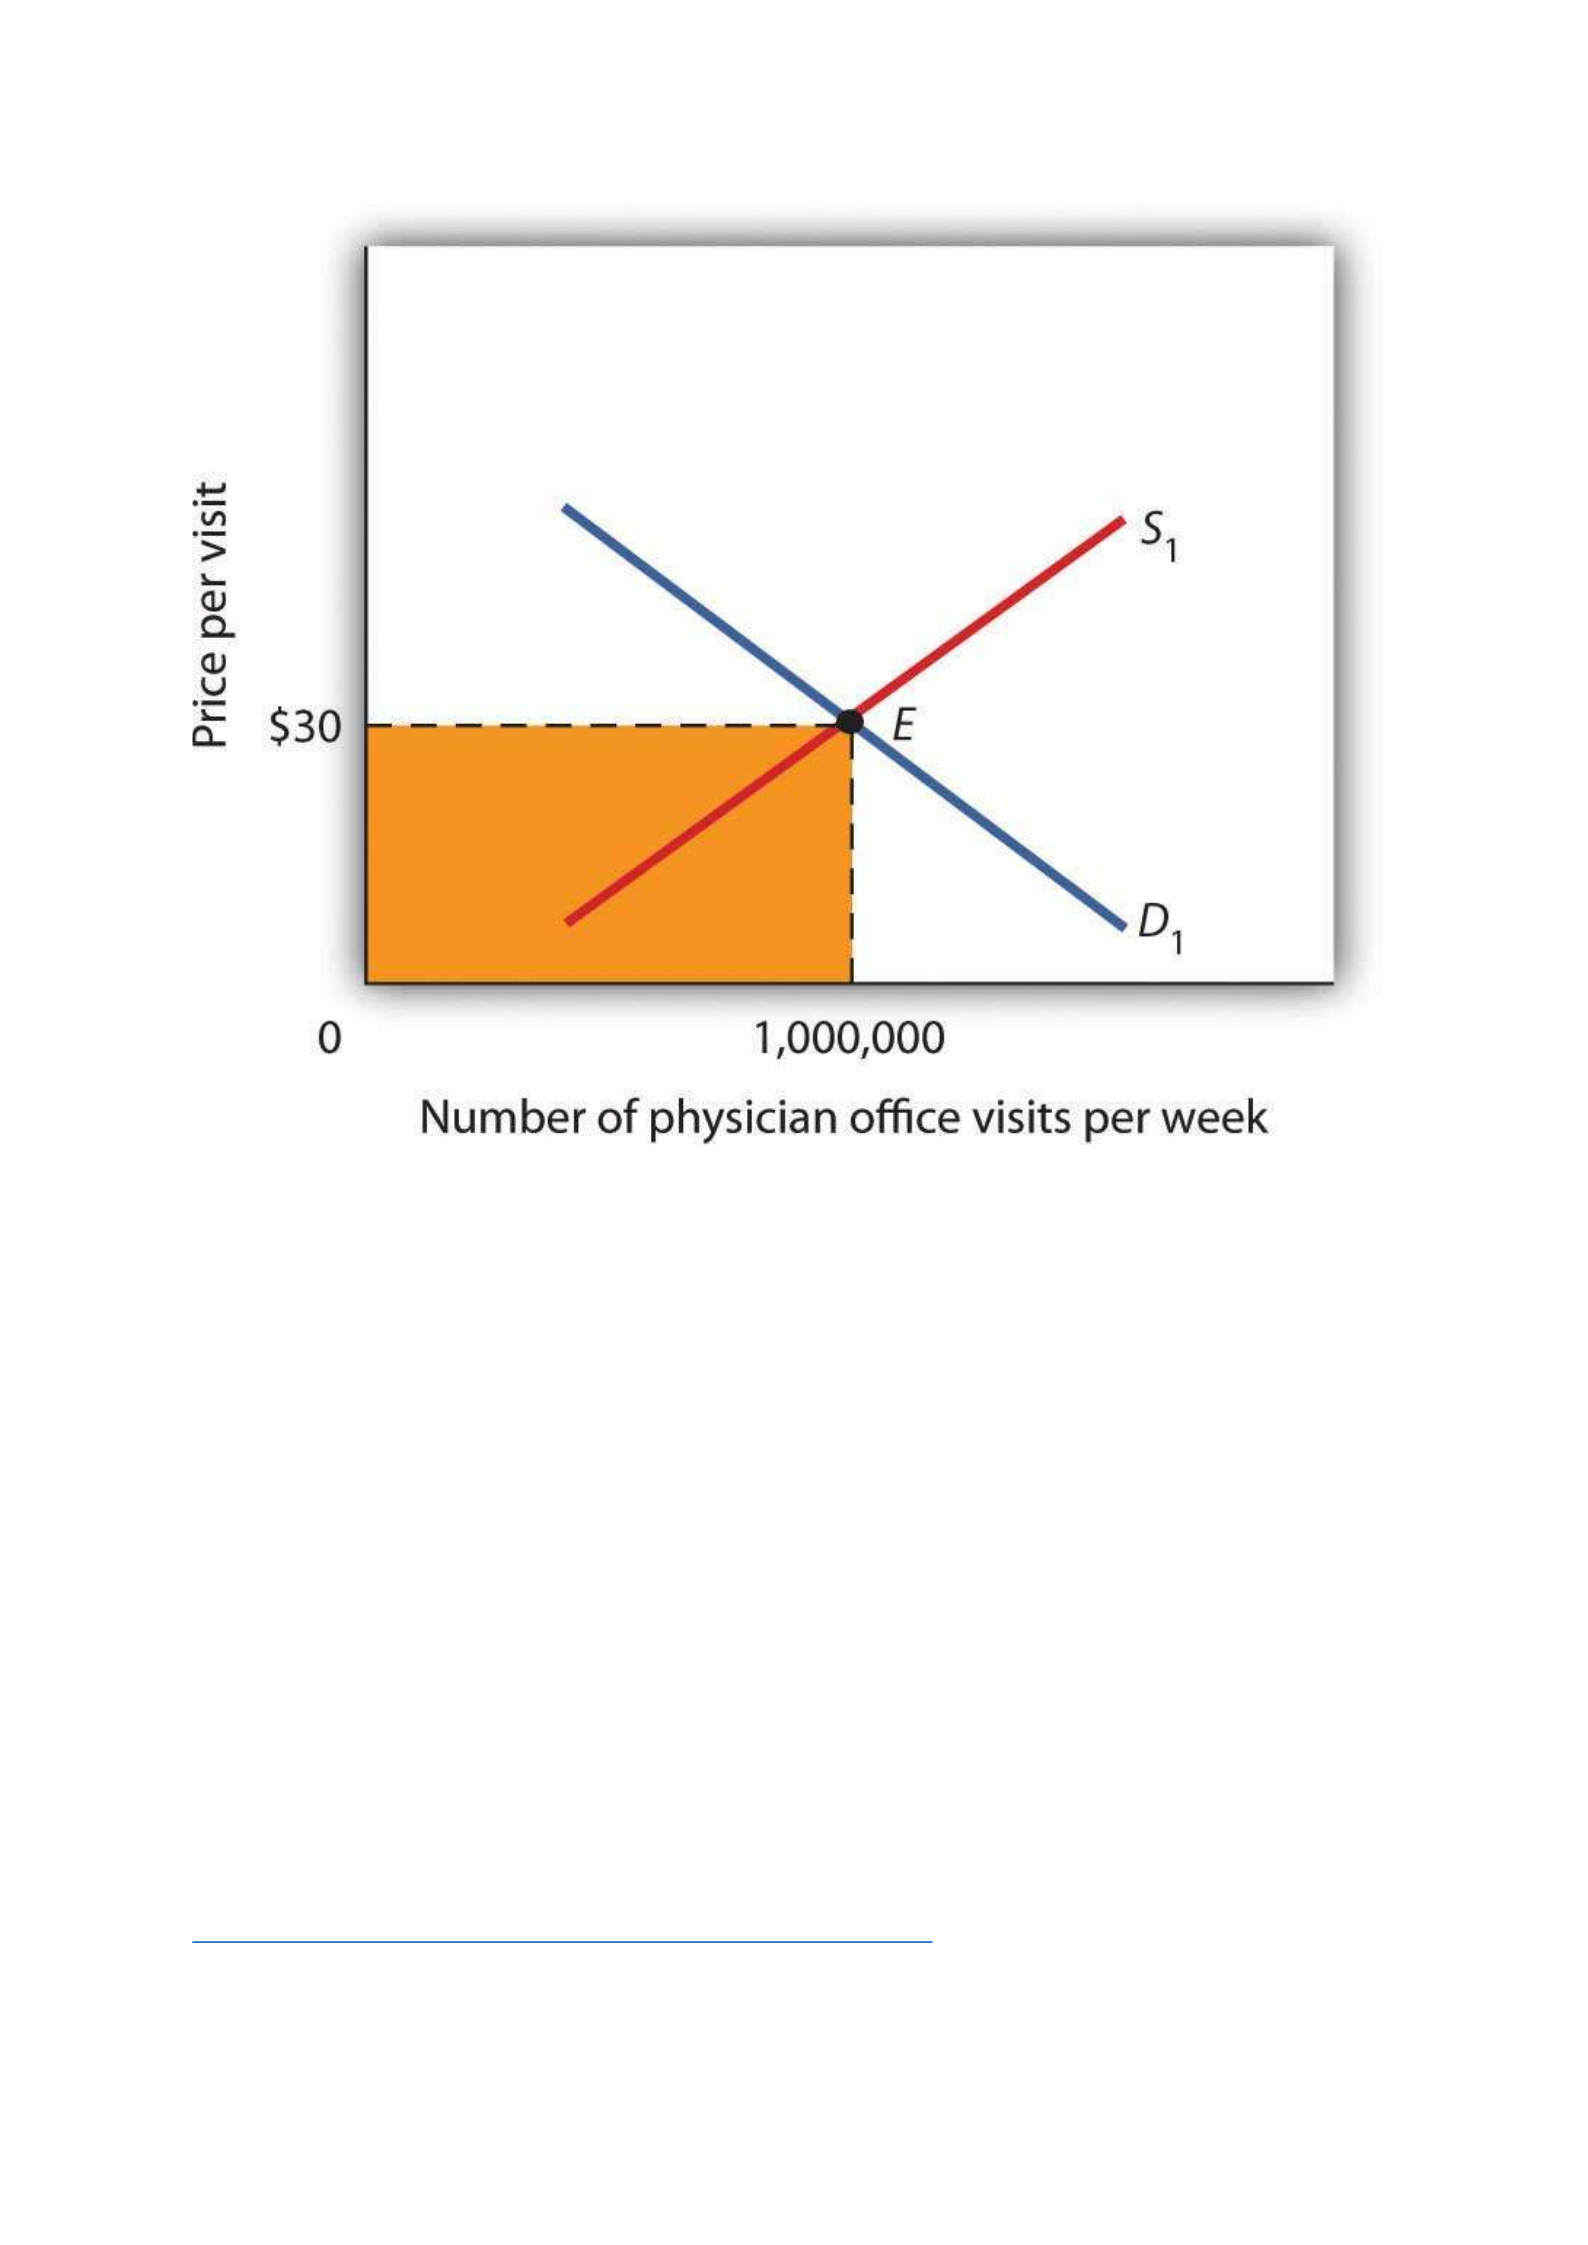
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
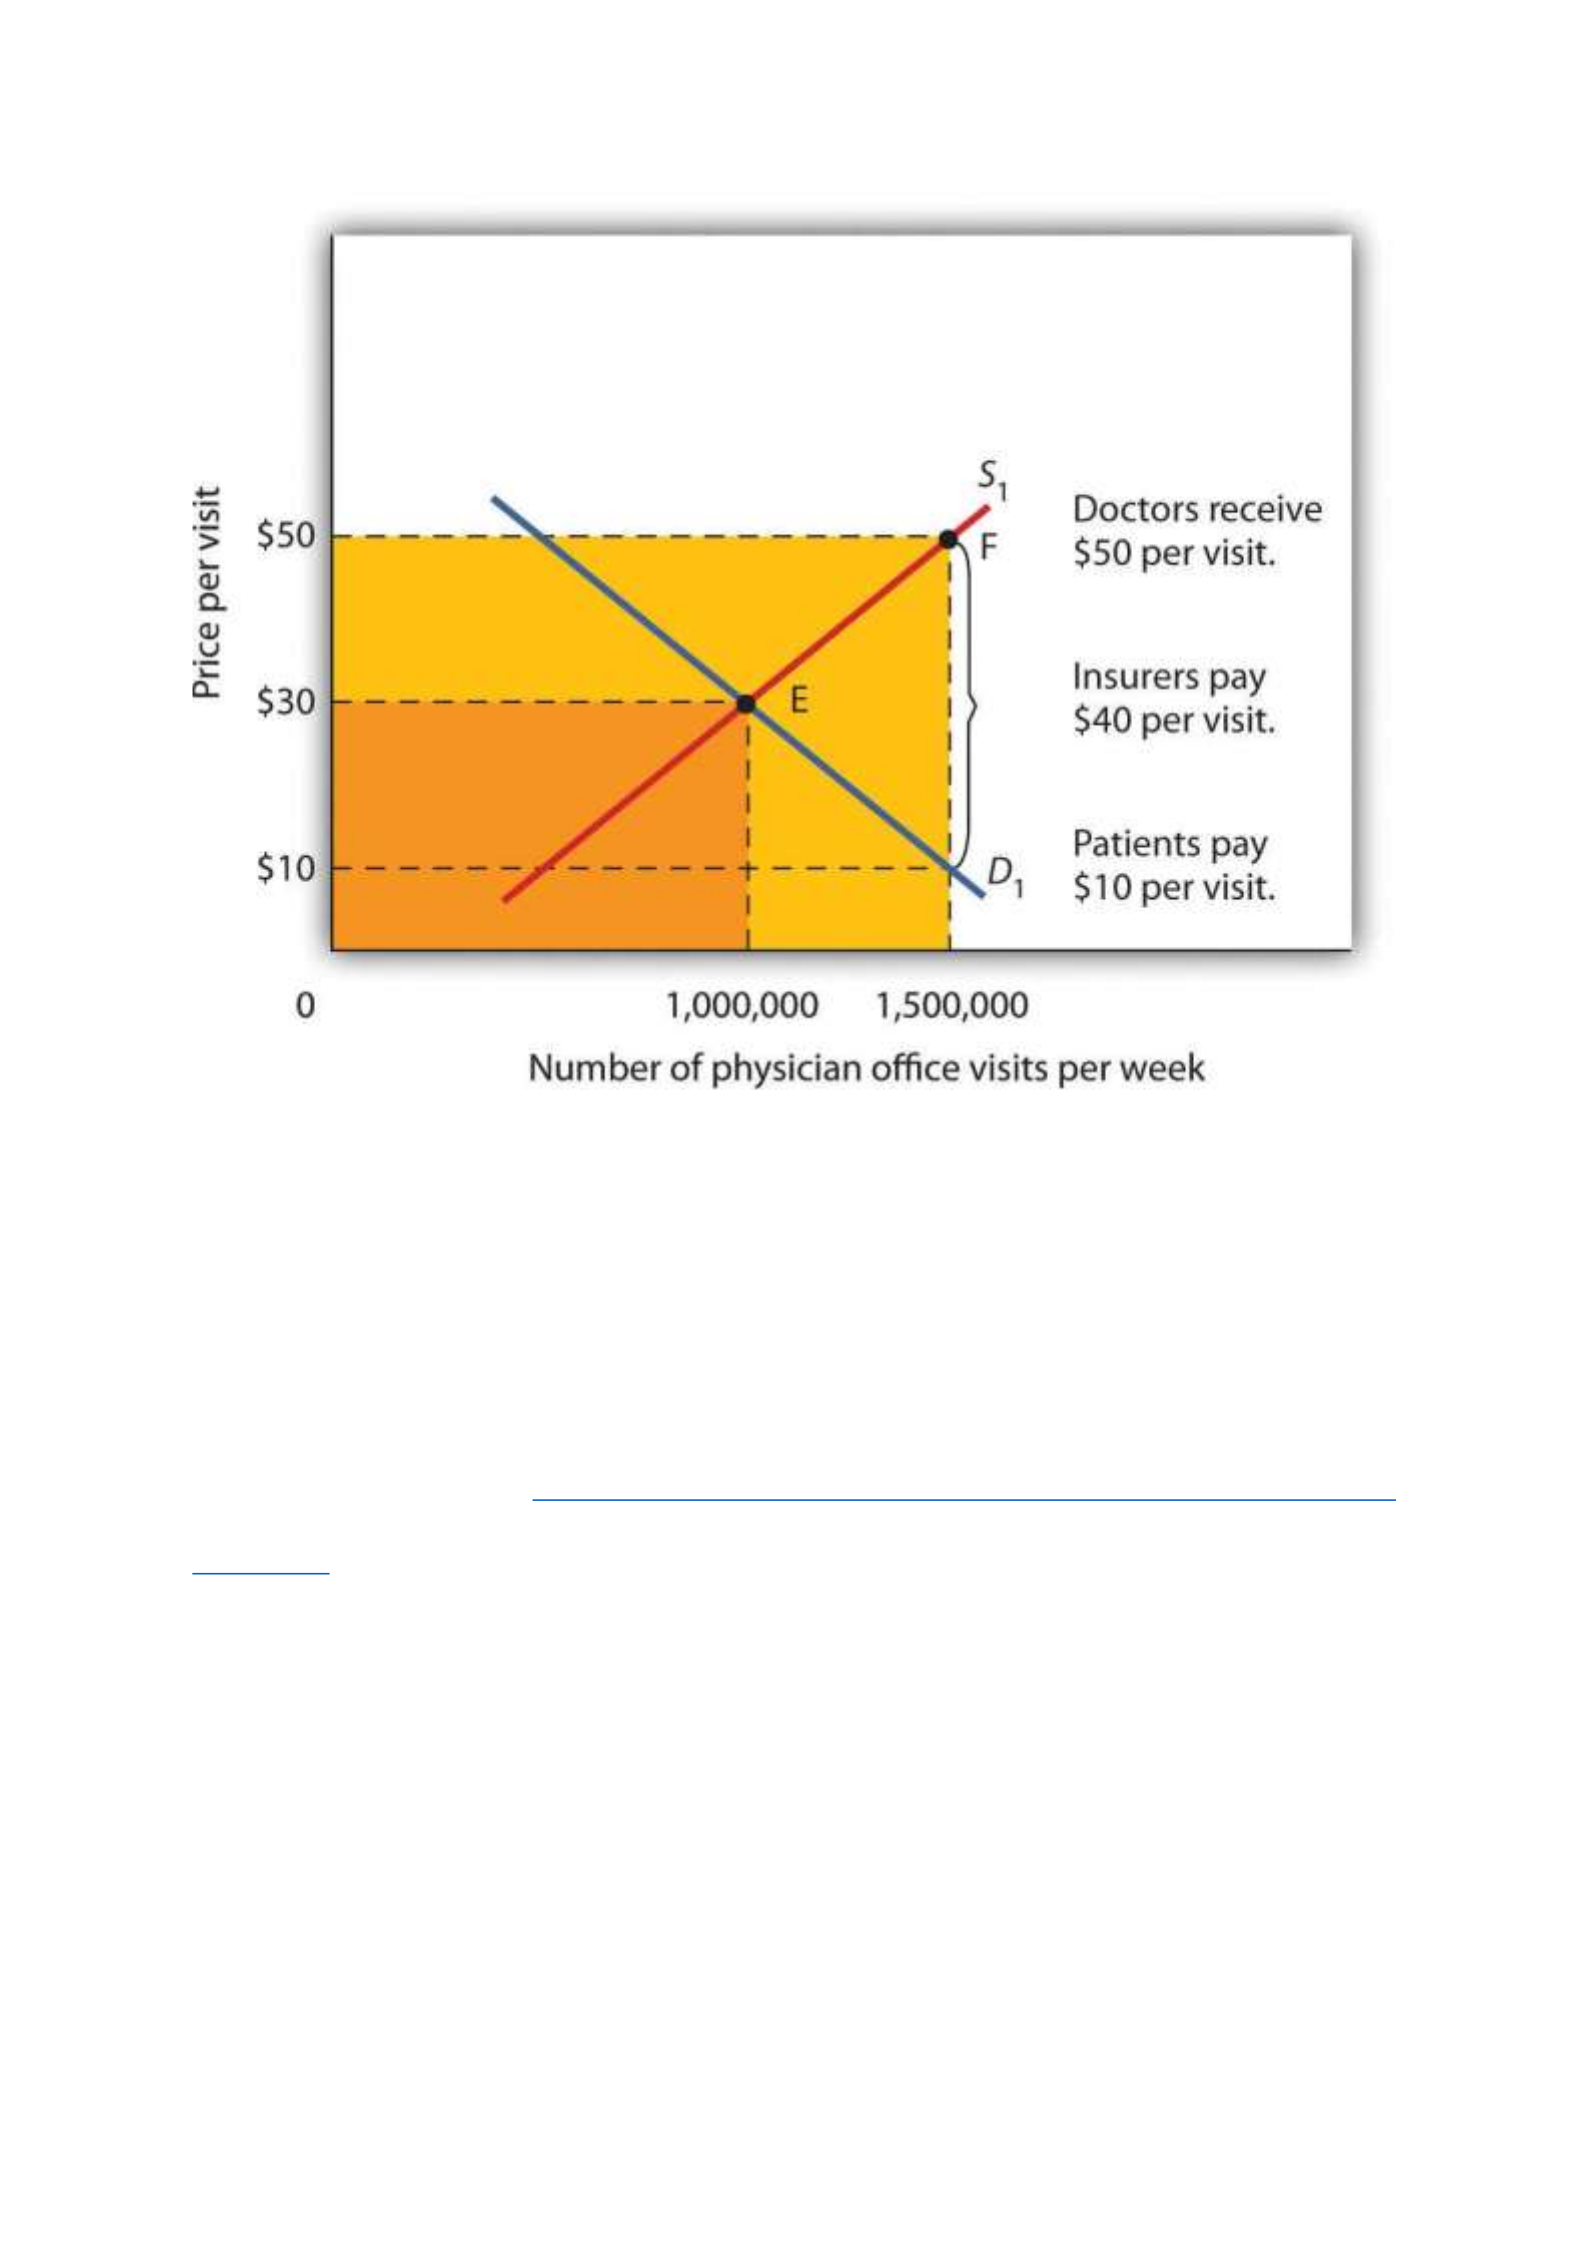
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
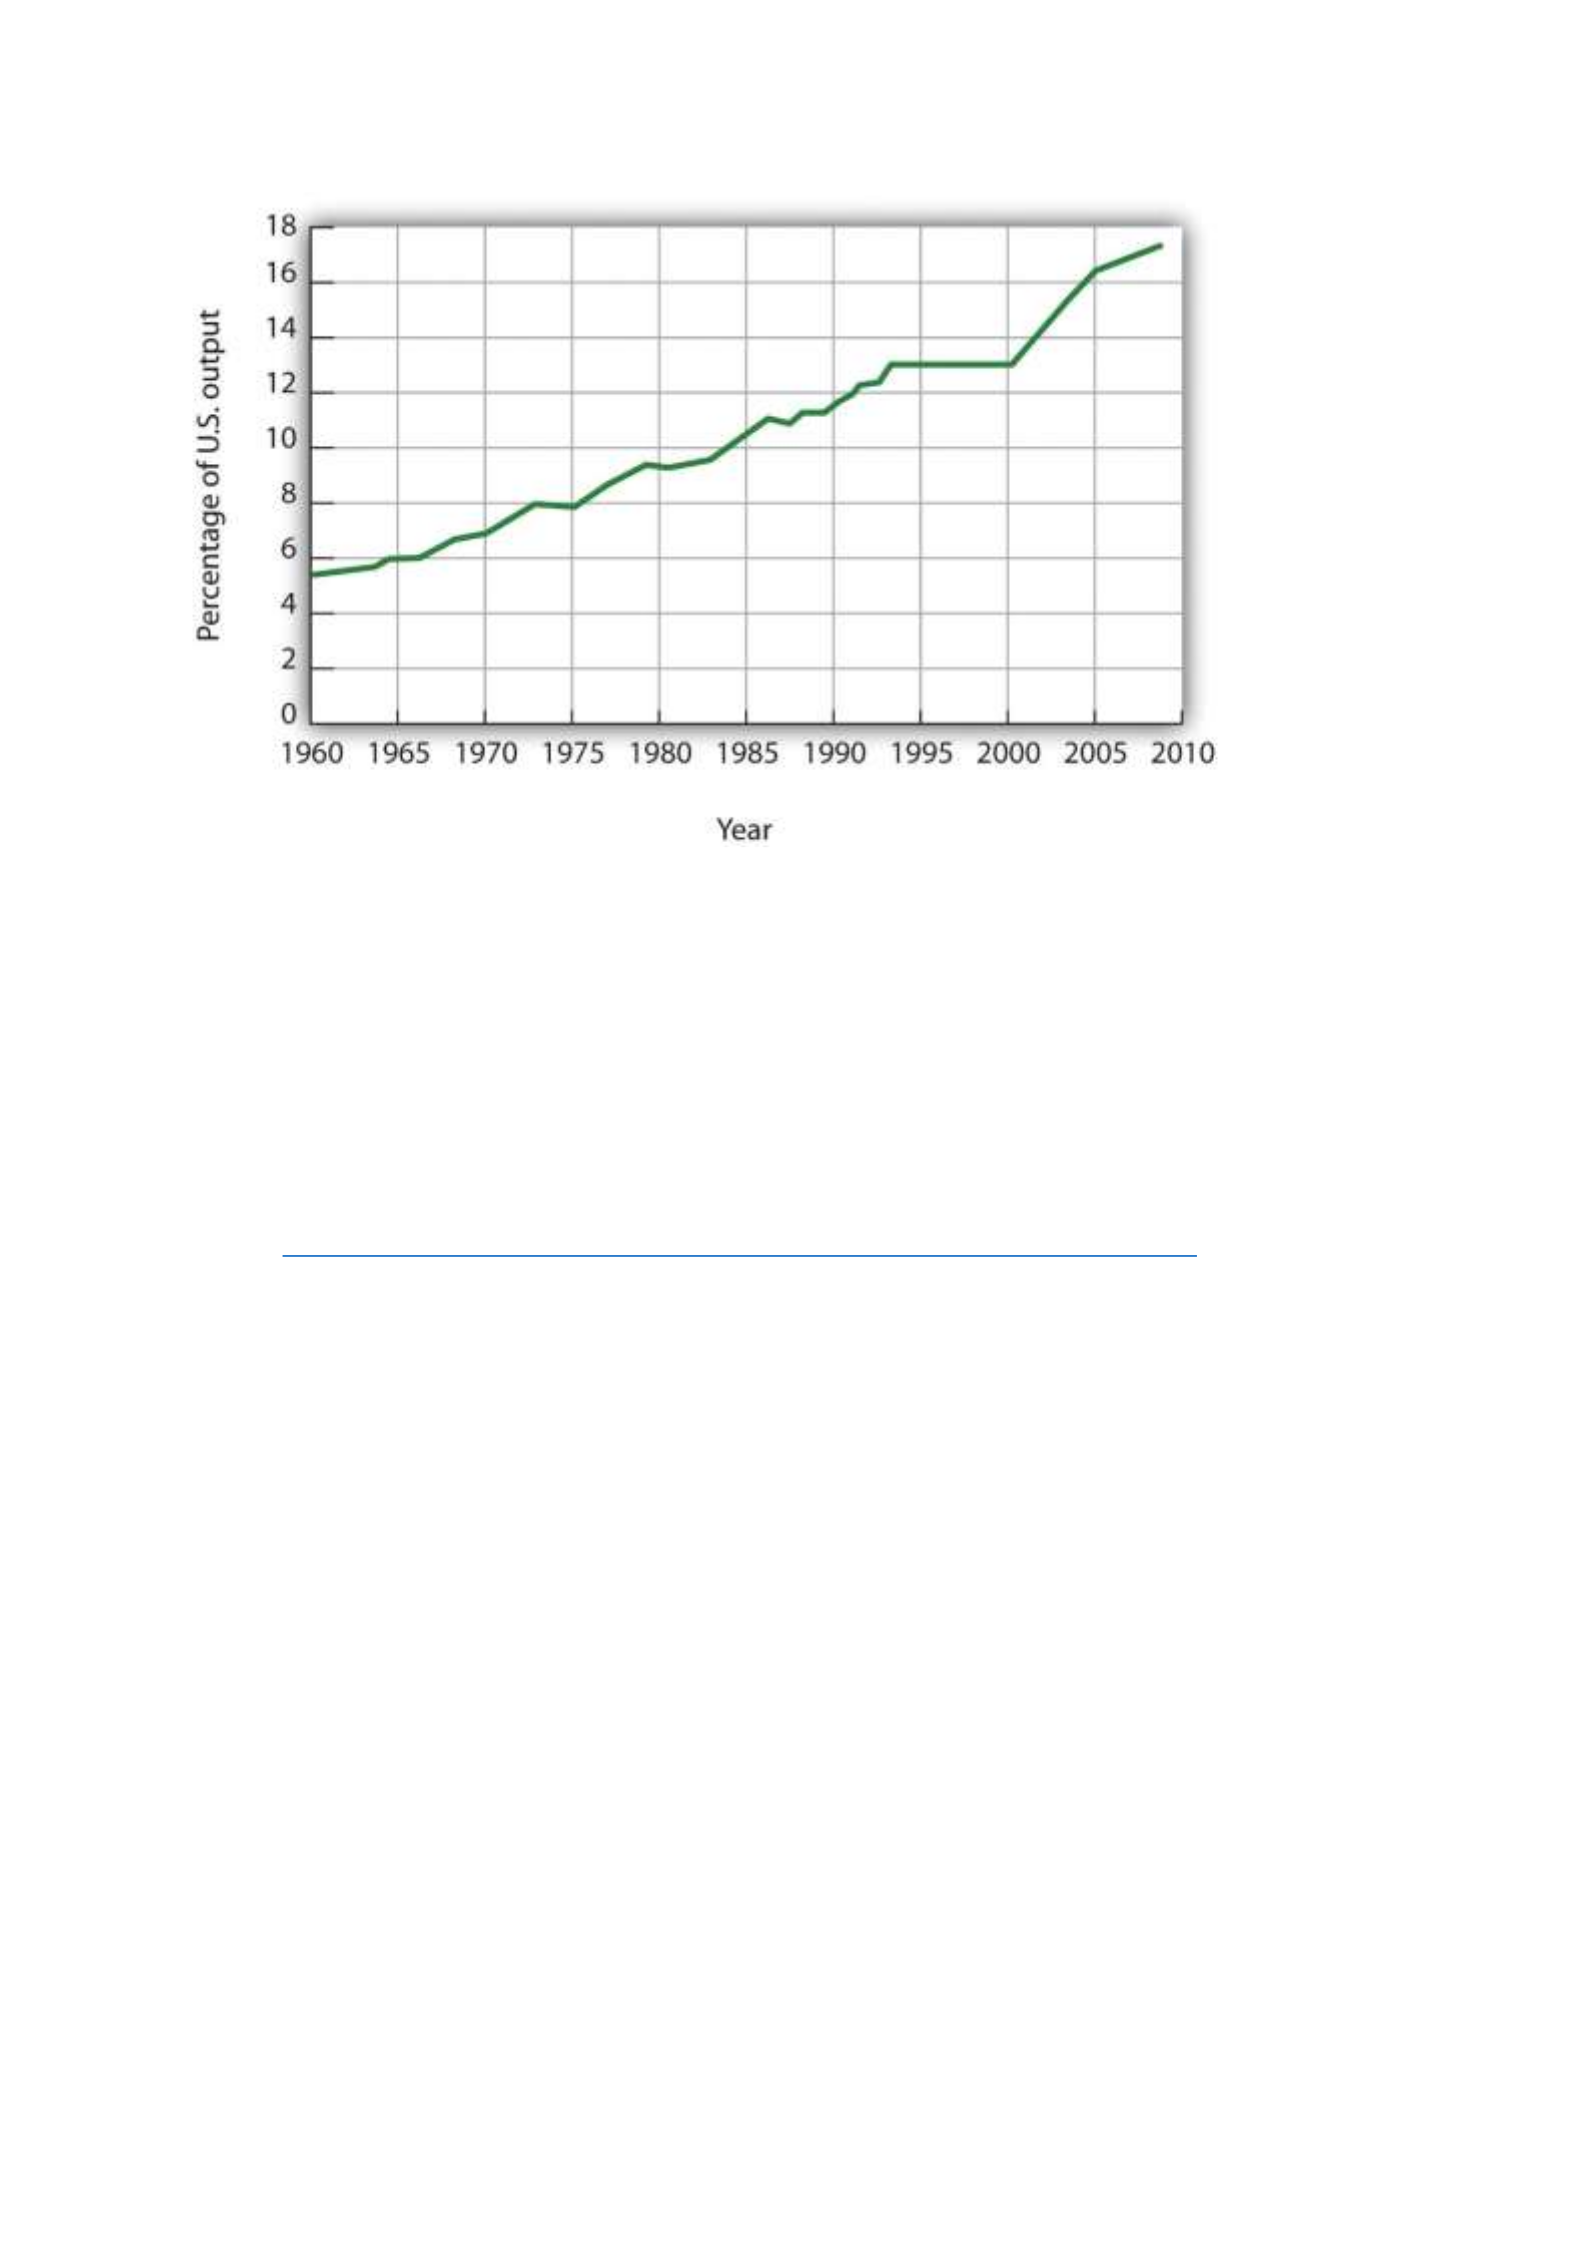
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
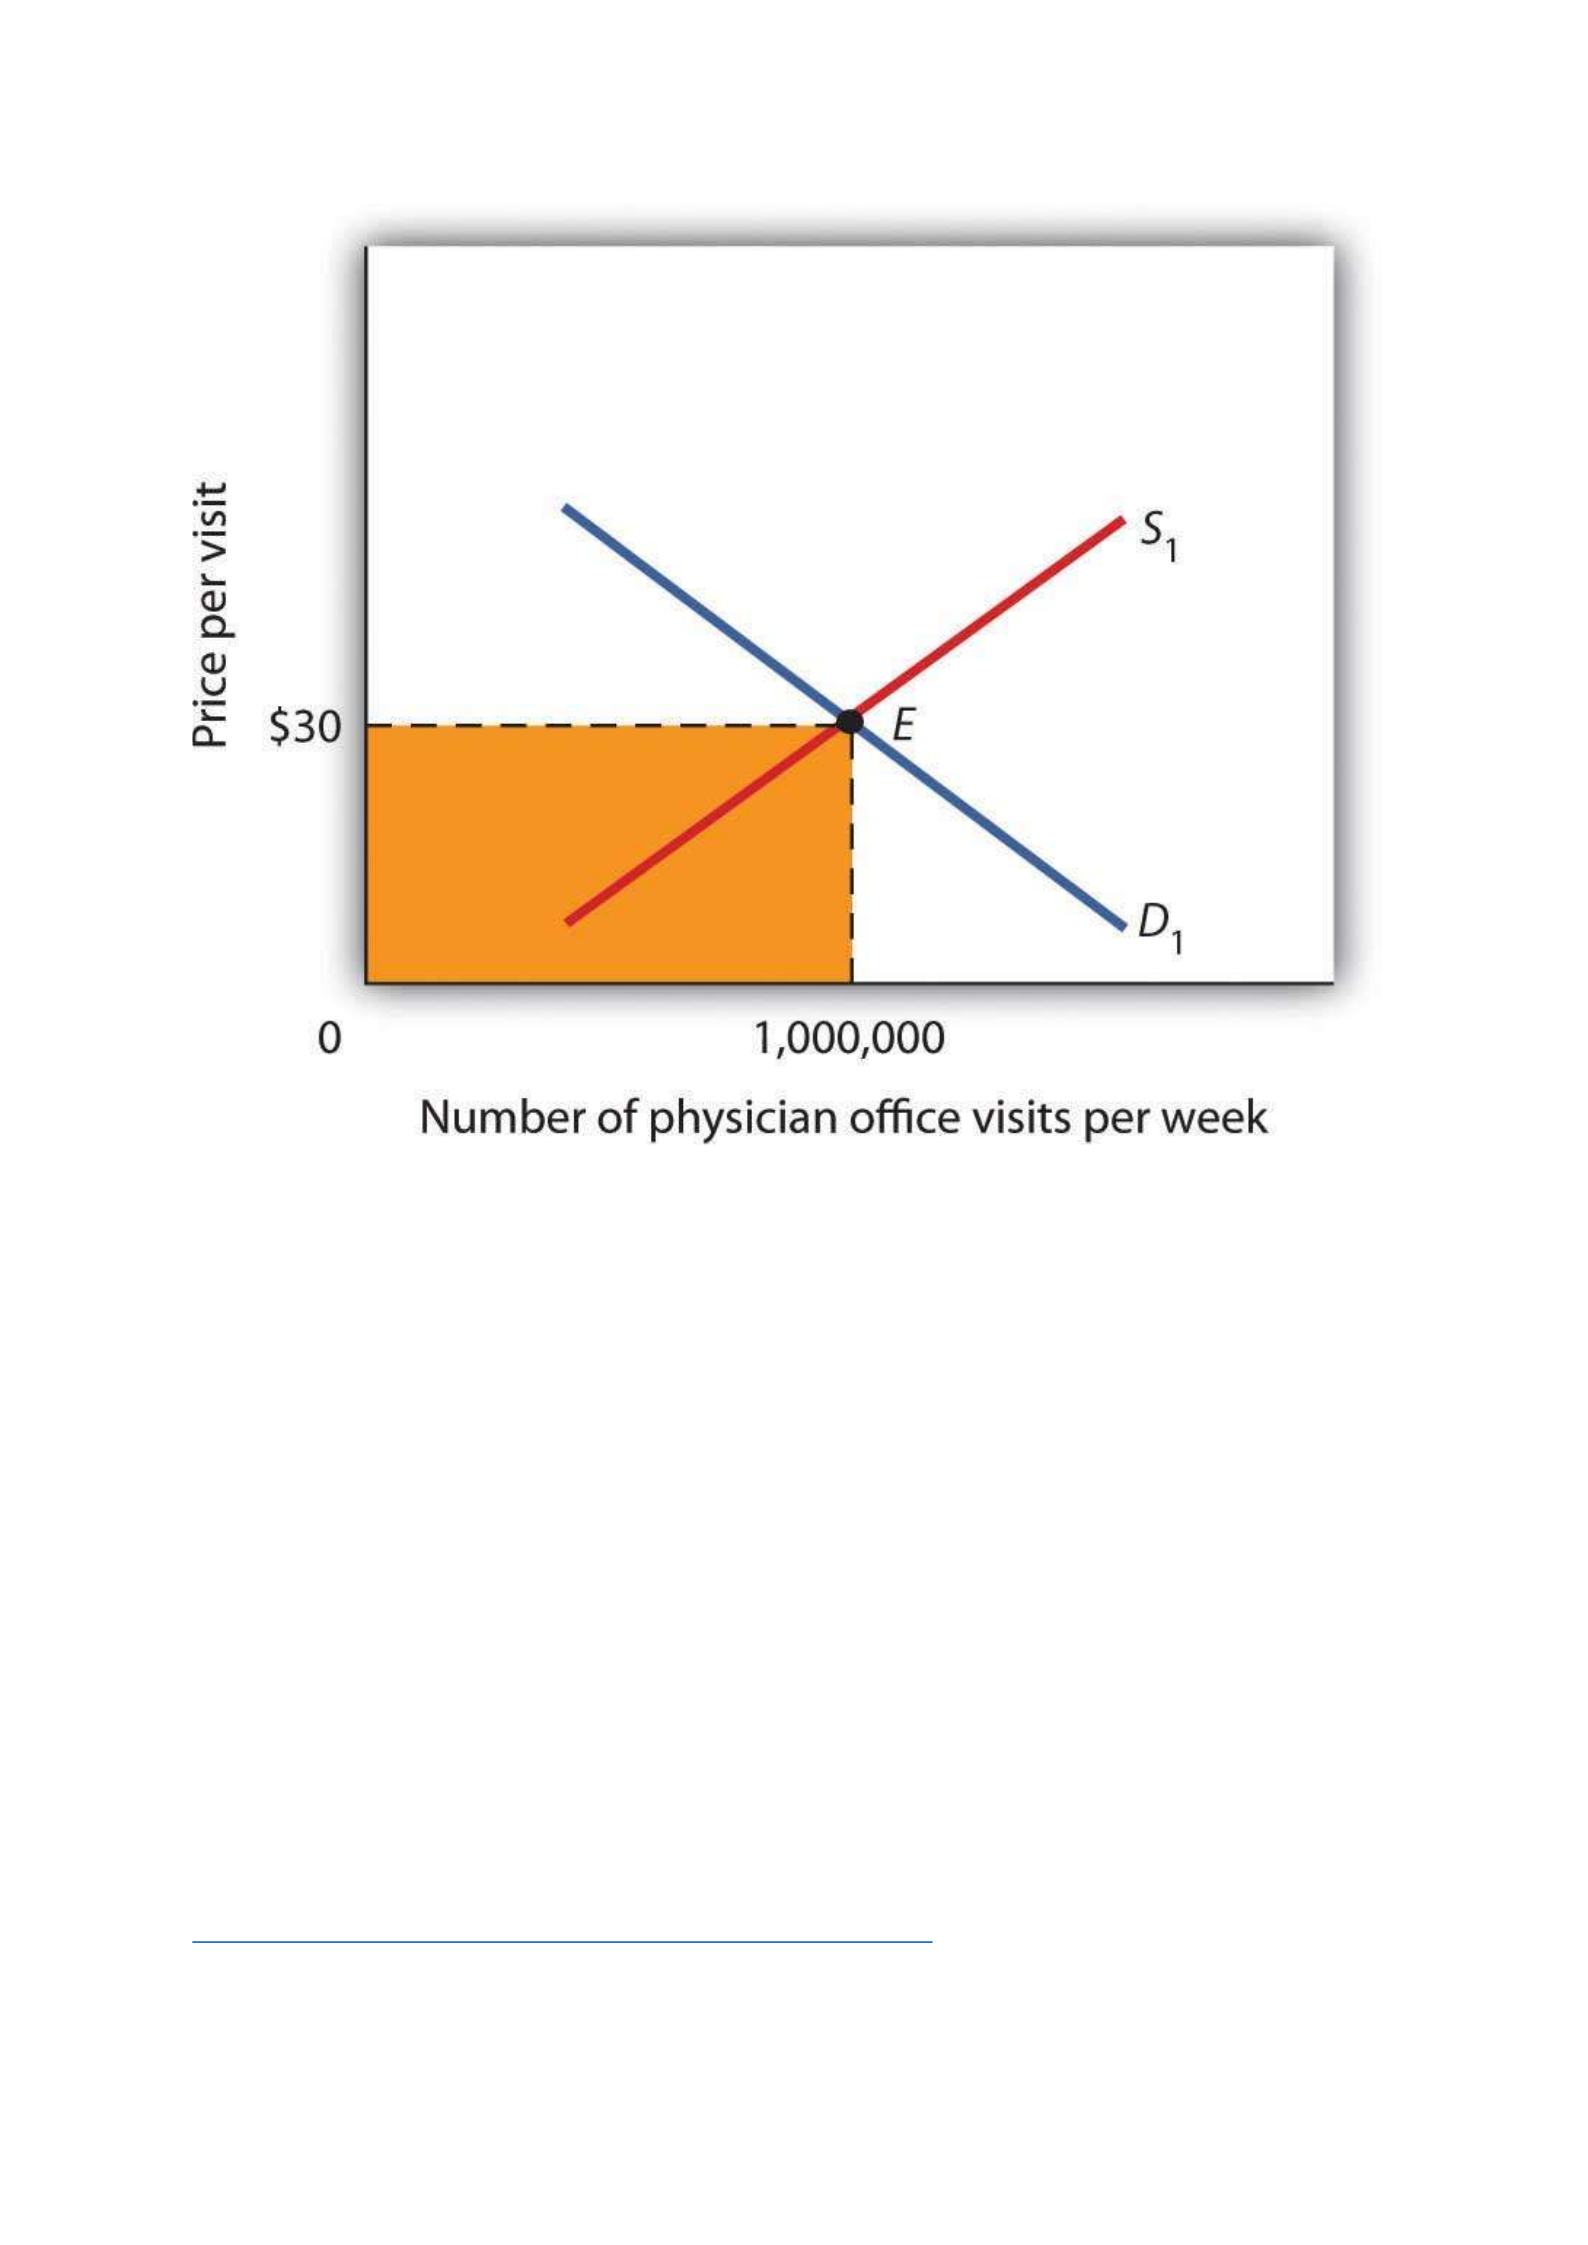
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
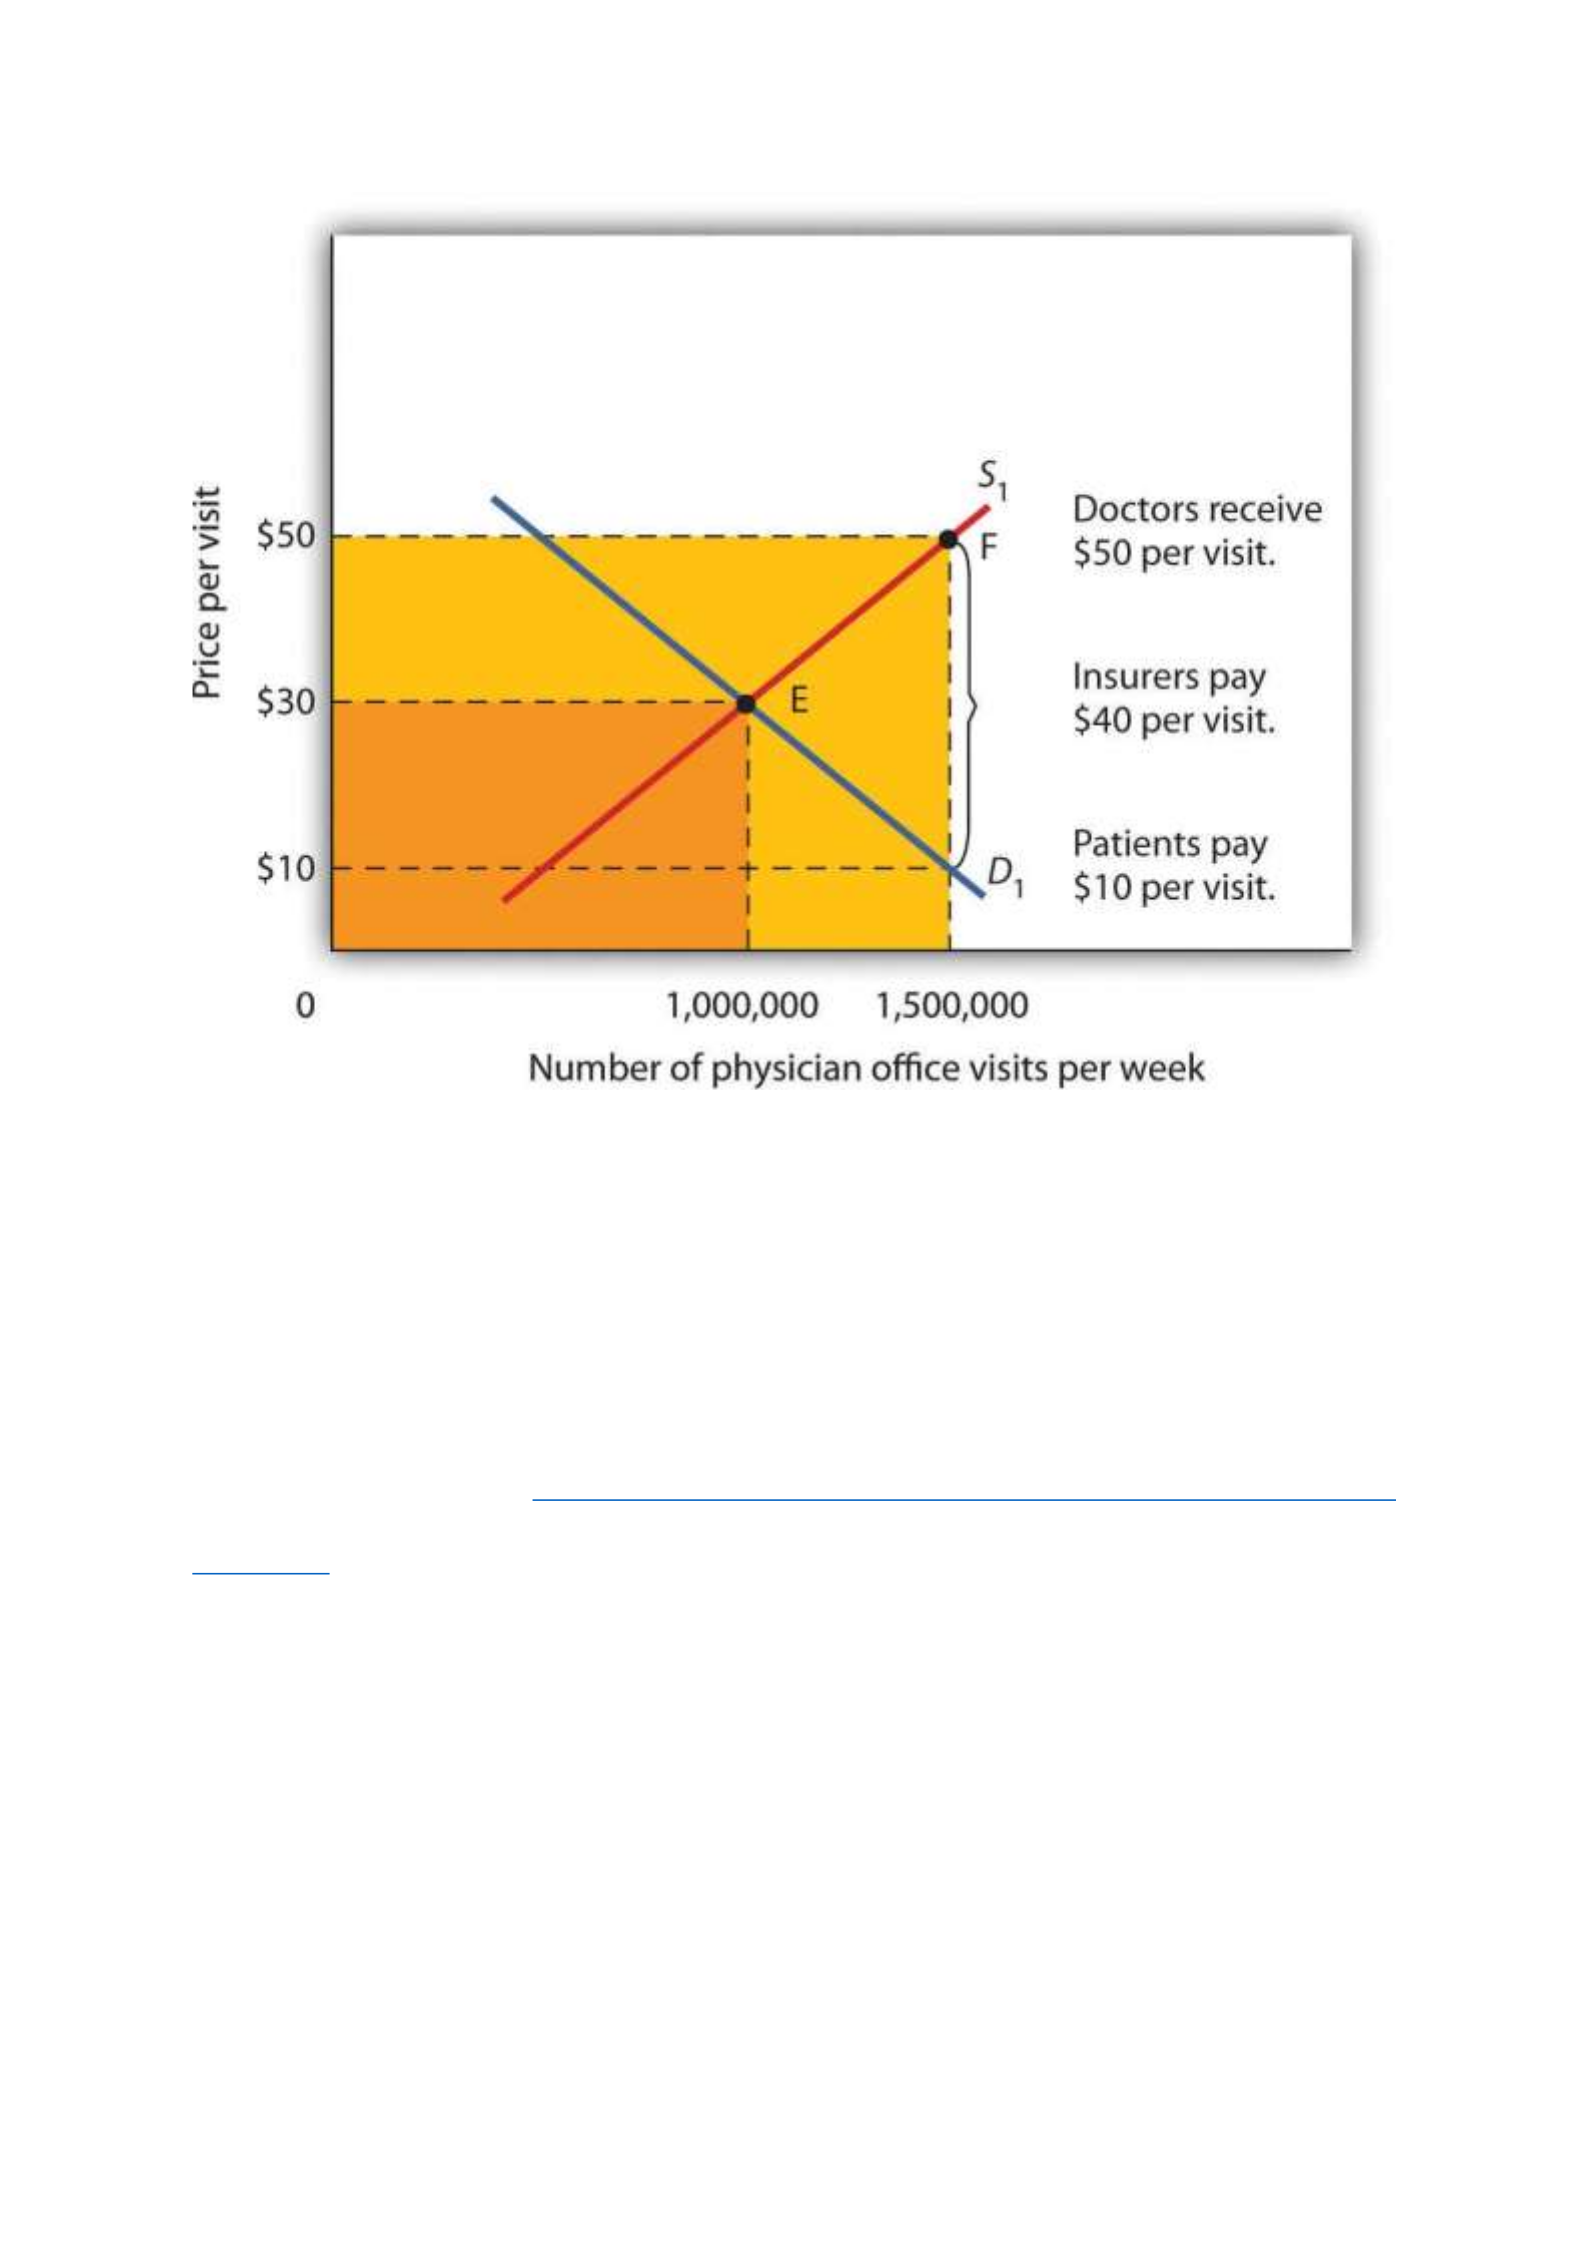
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
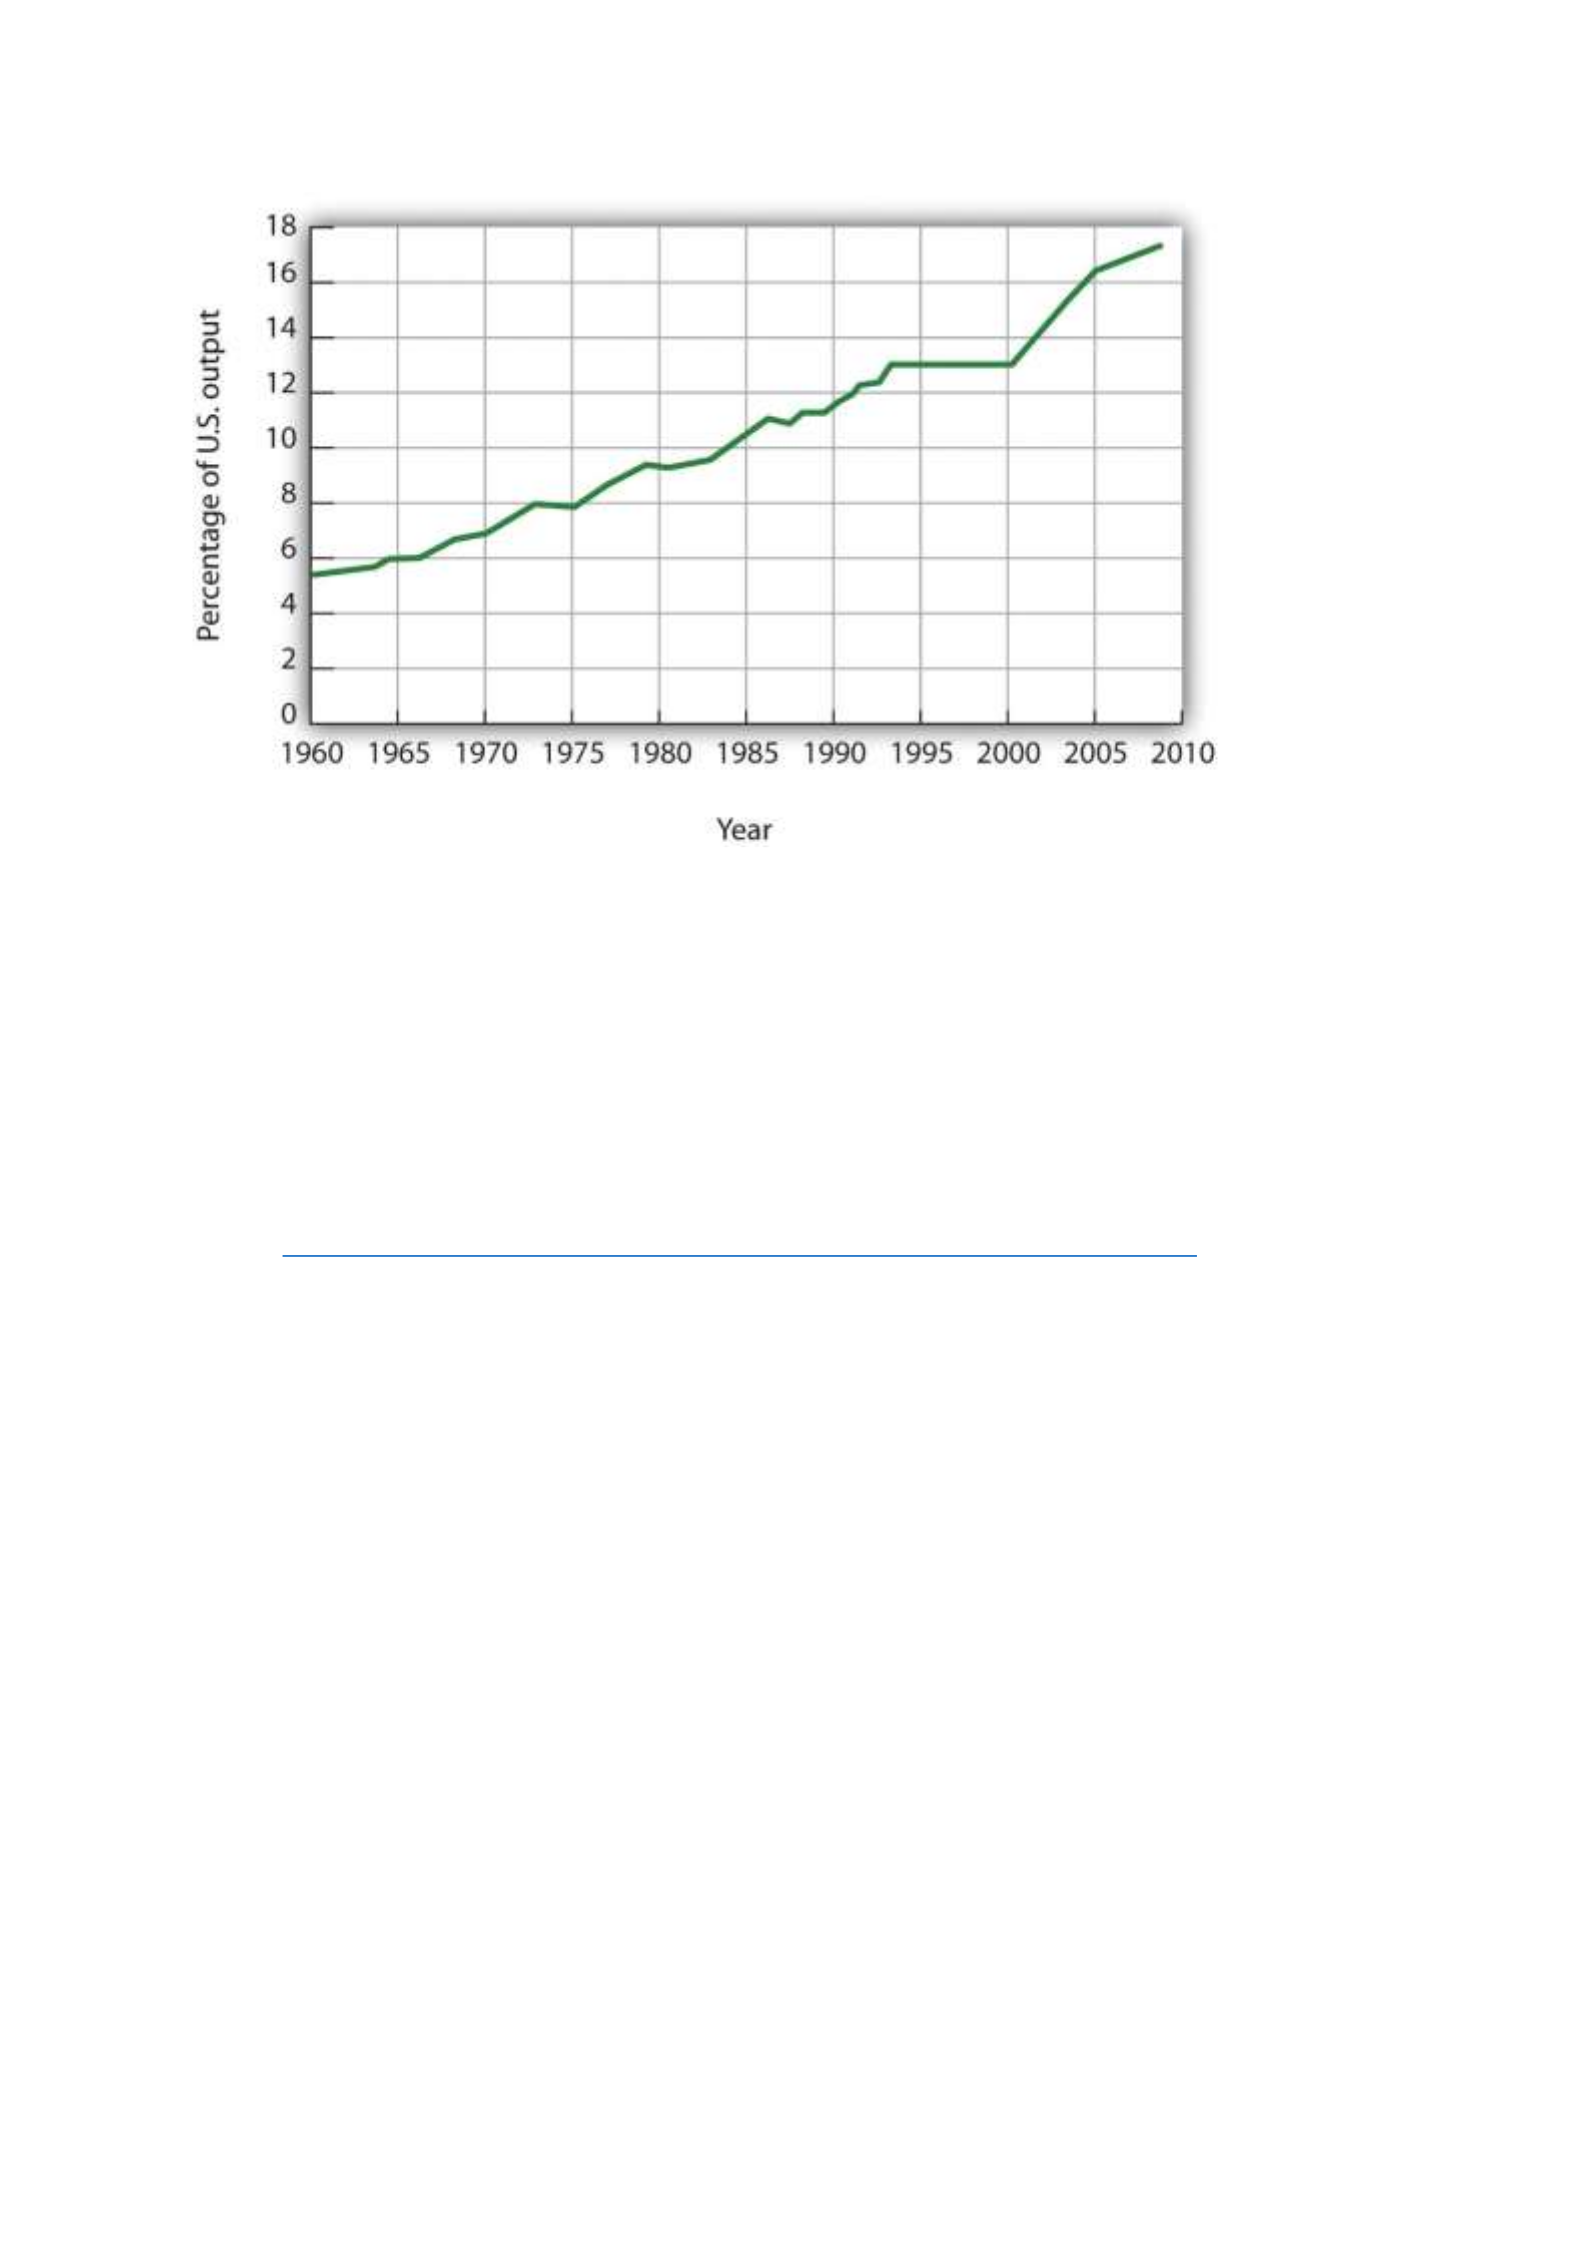
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
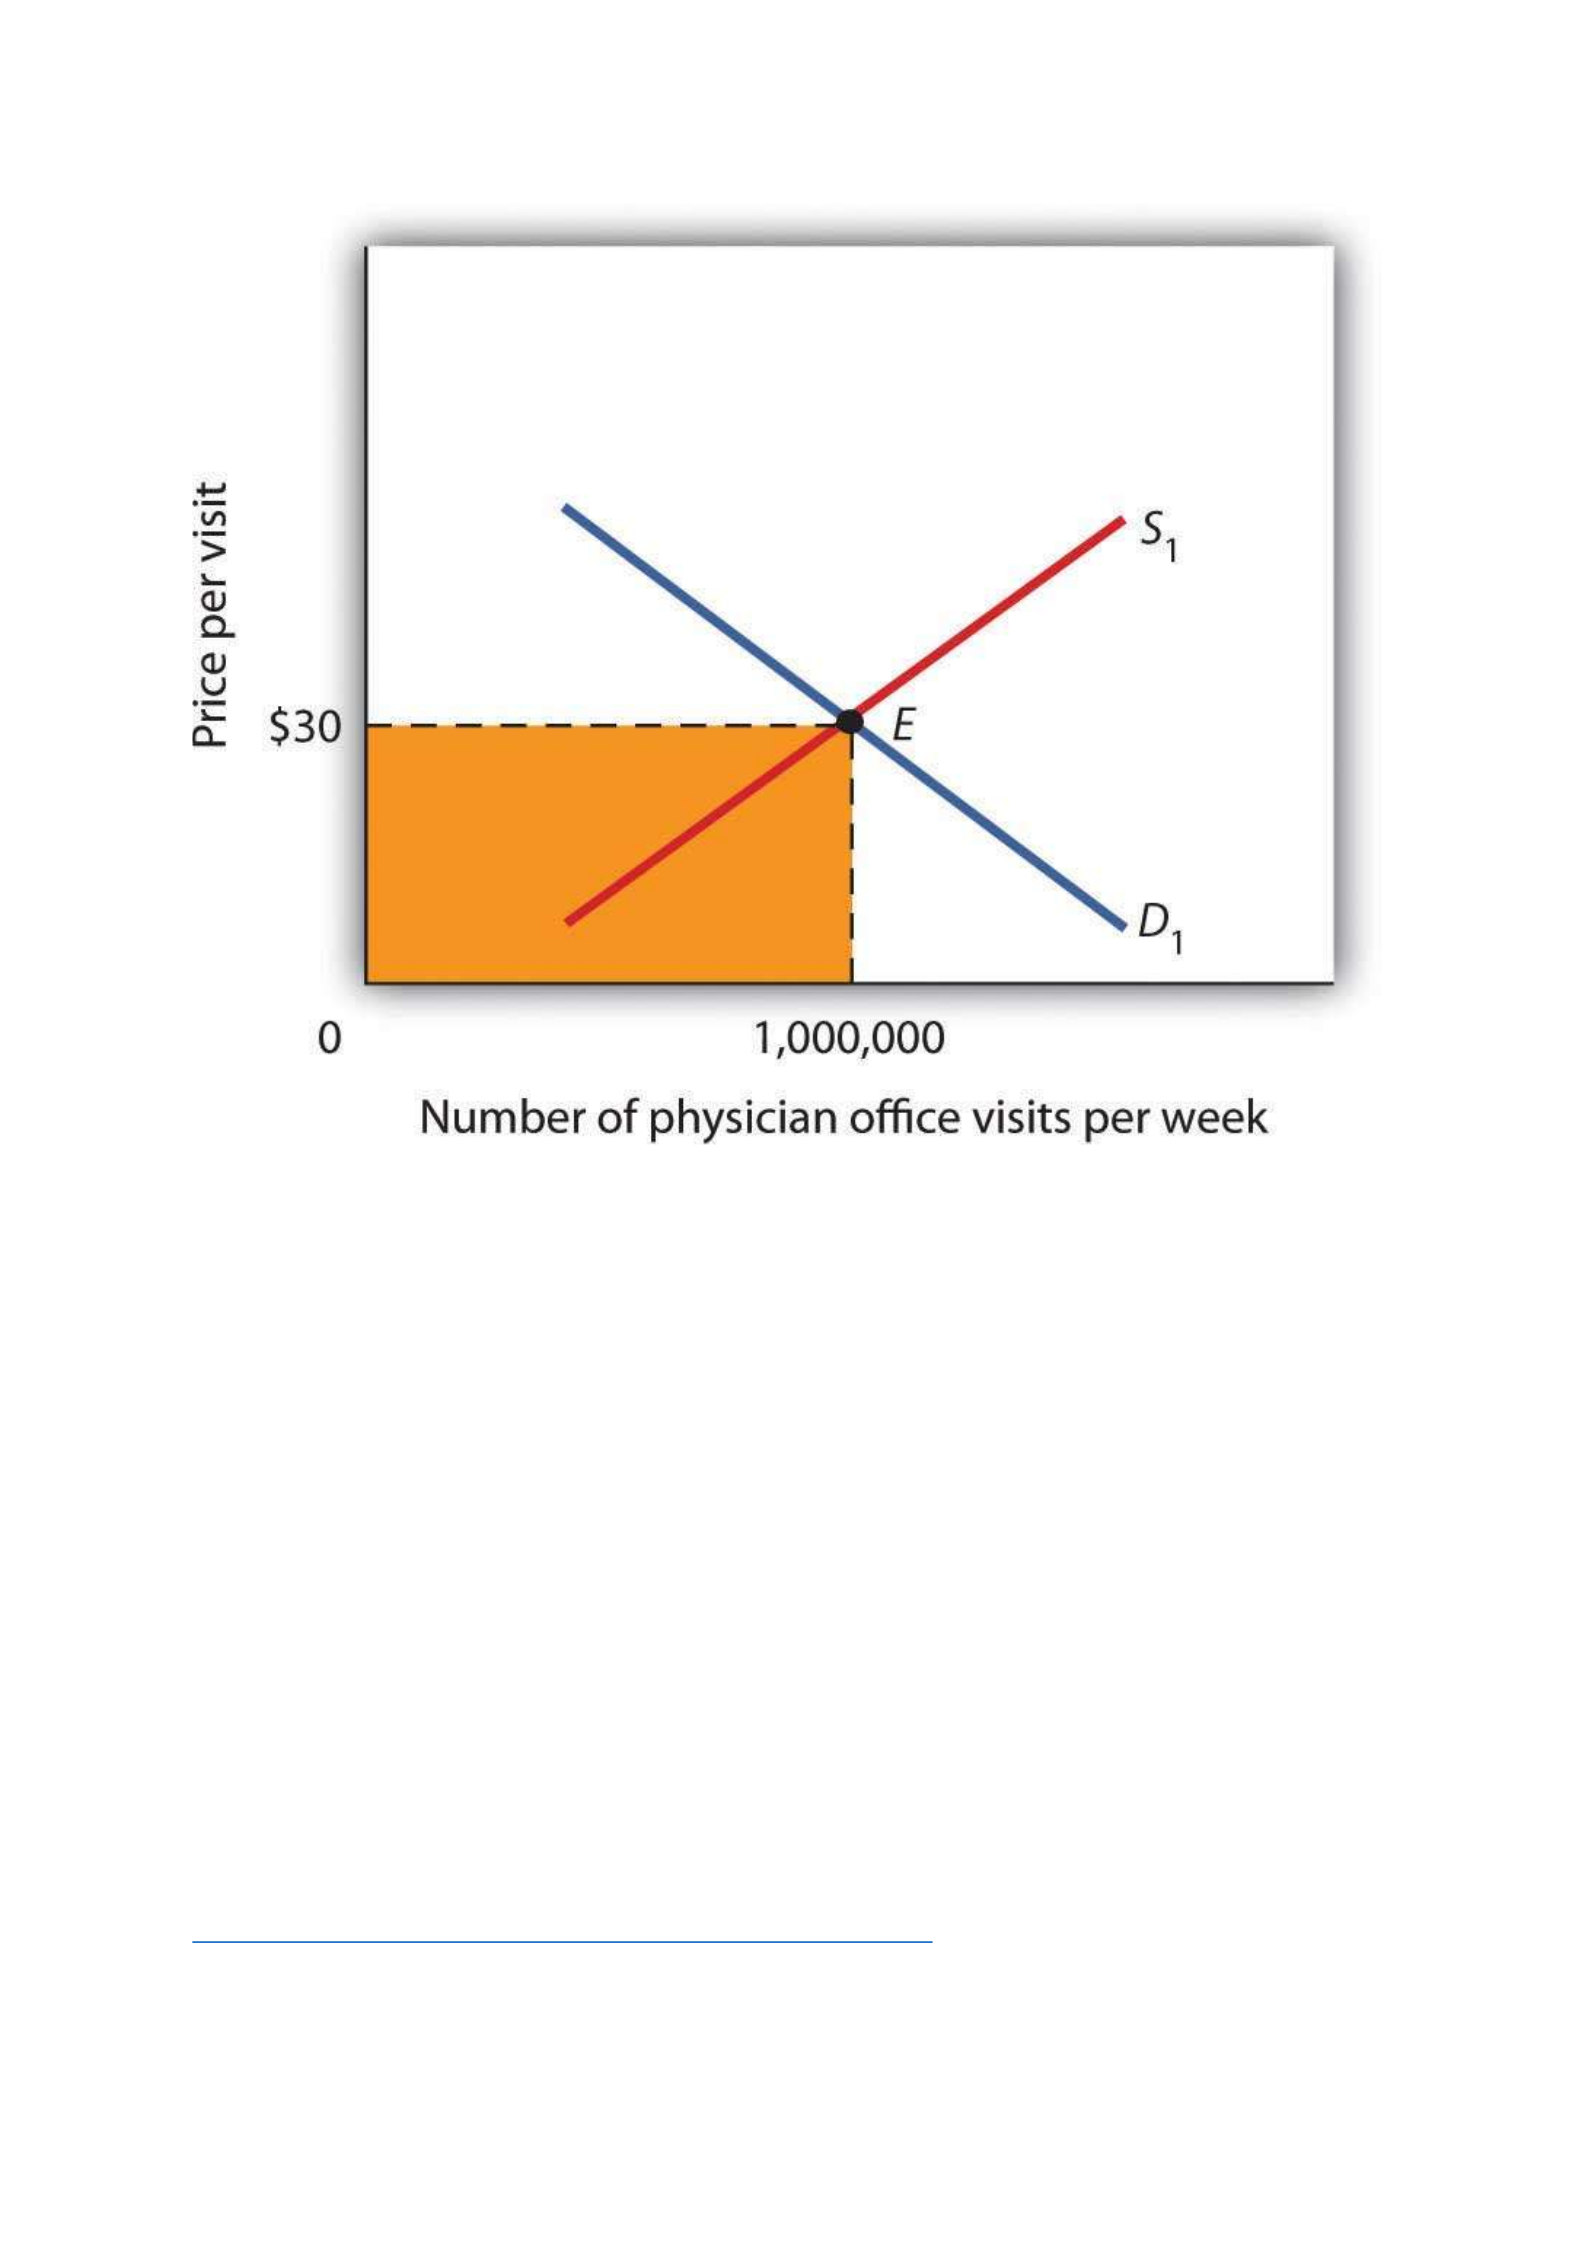
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
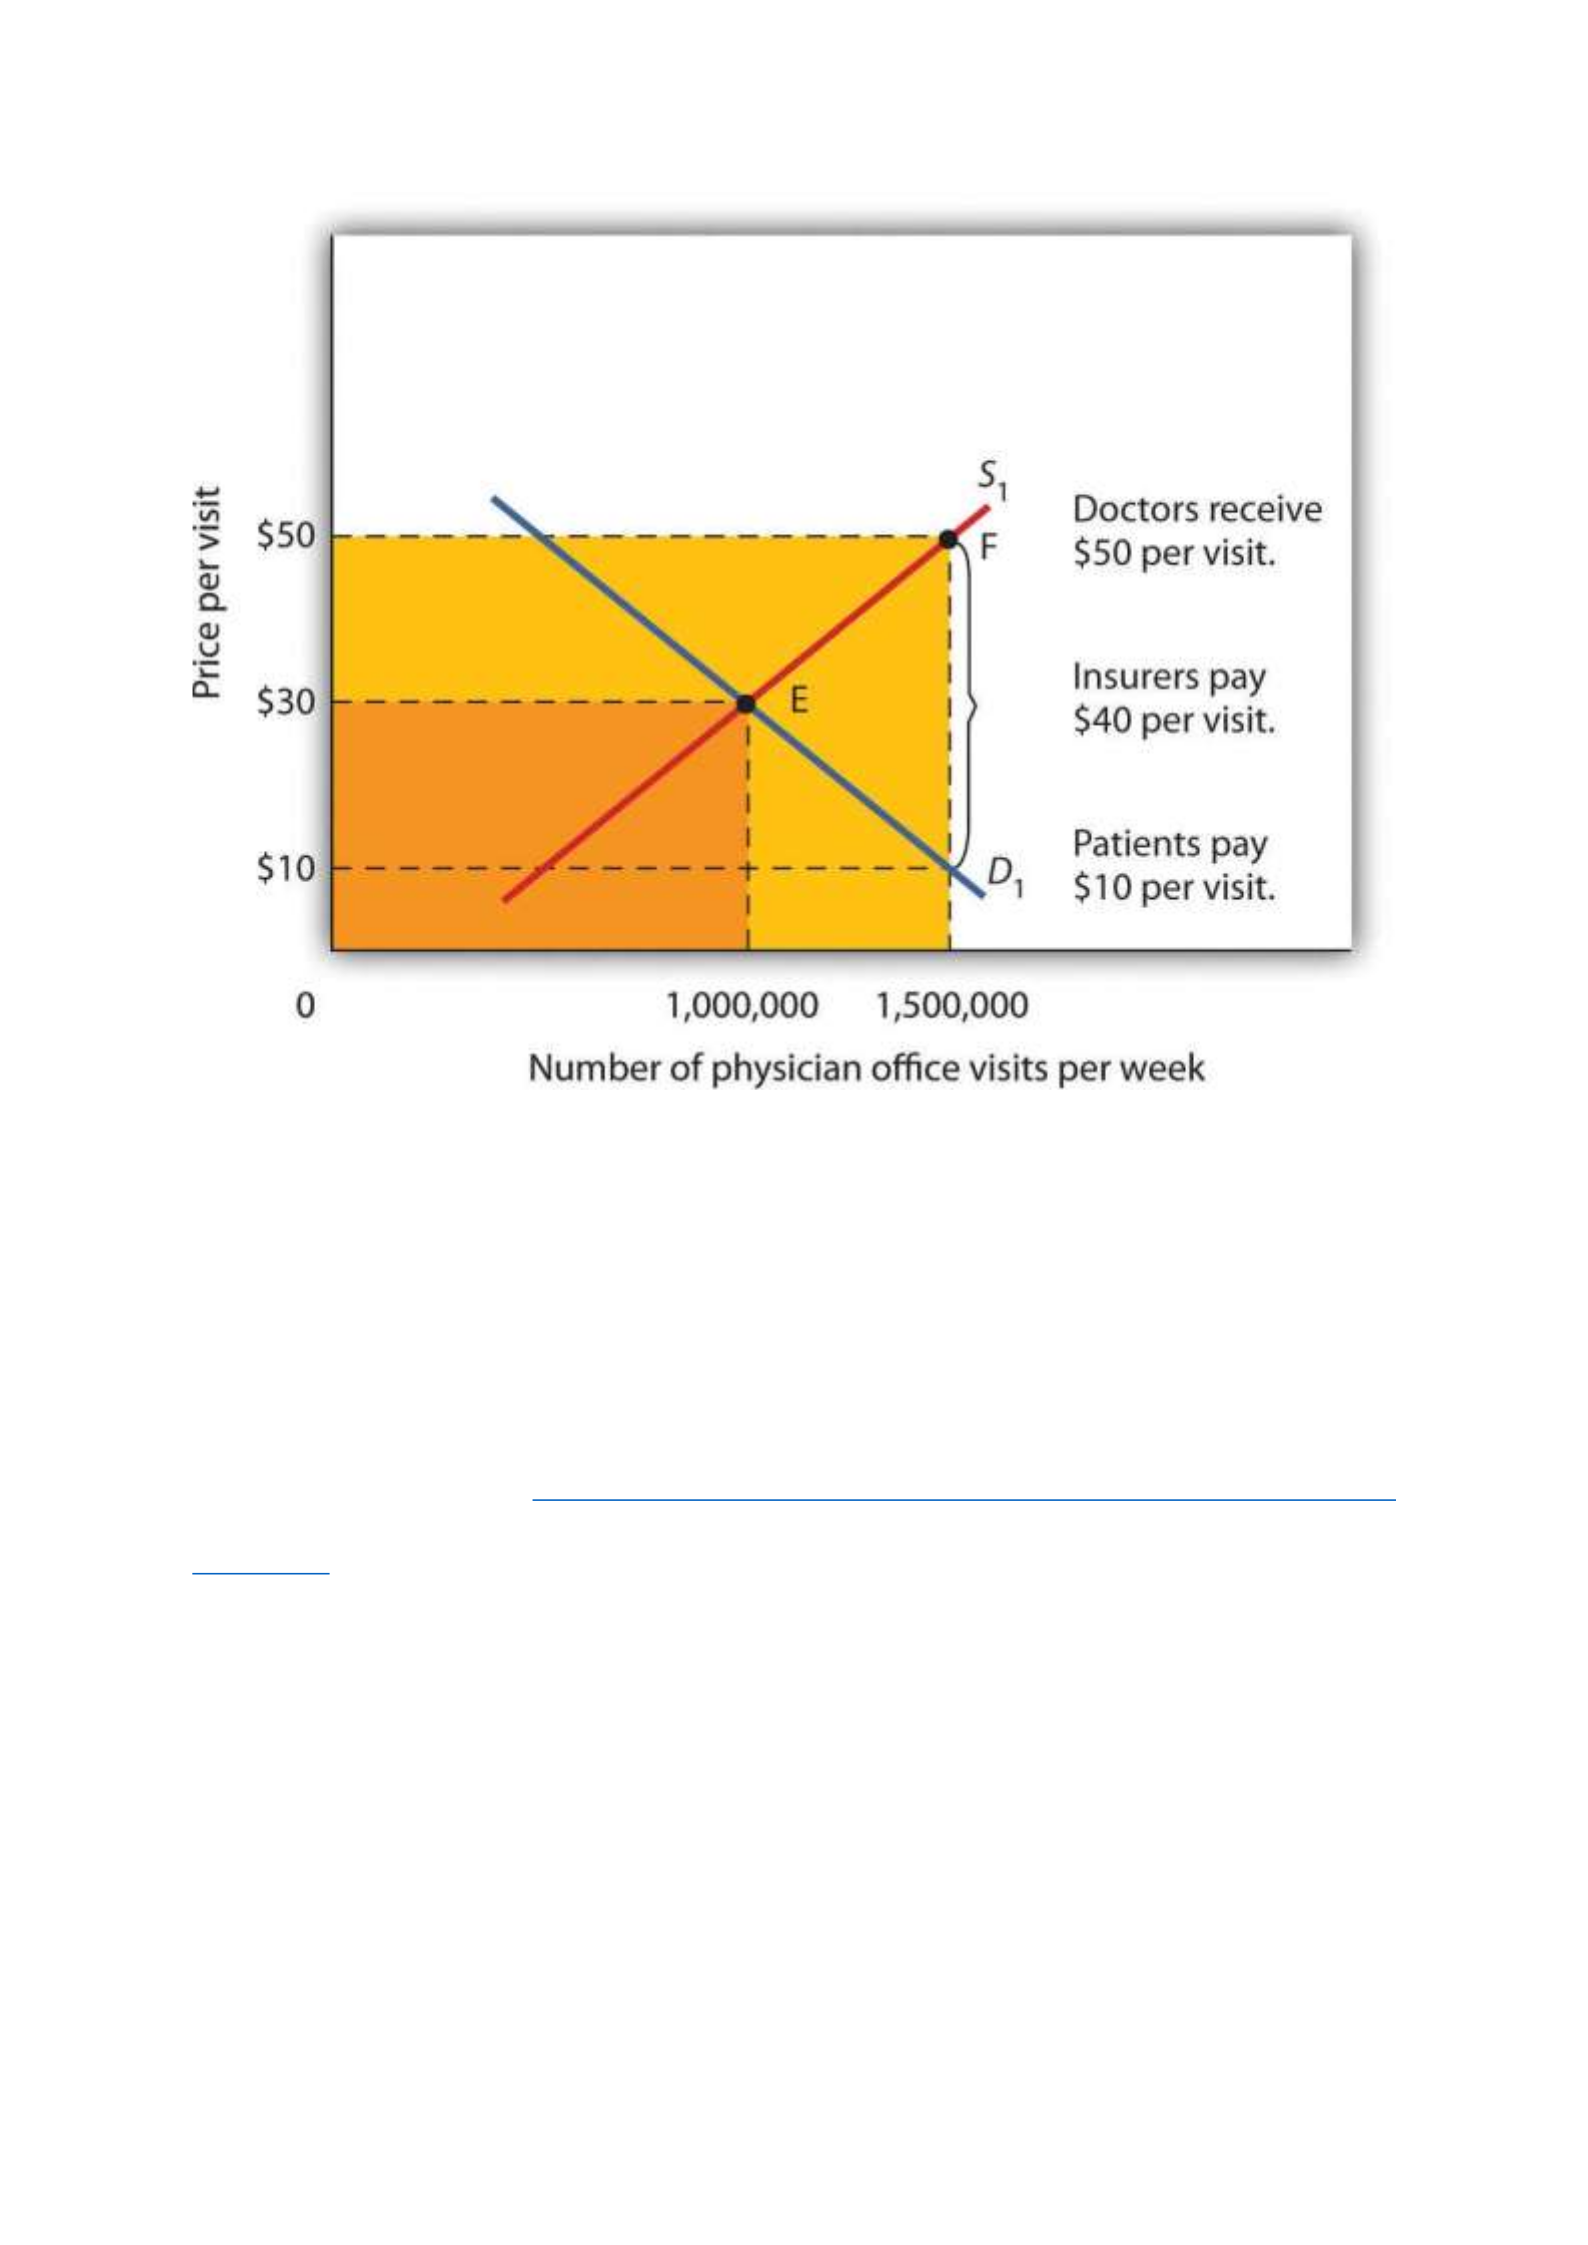
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending. There has
been much discussion over the past three decades about the health-care problem in the United
States. Much of this discussion has focused on rising spending for health care. In this section,
we will apply the model of demand and supply to health care to see what we can learn about
some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
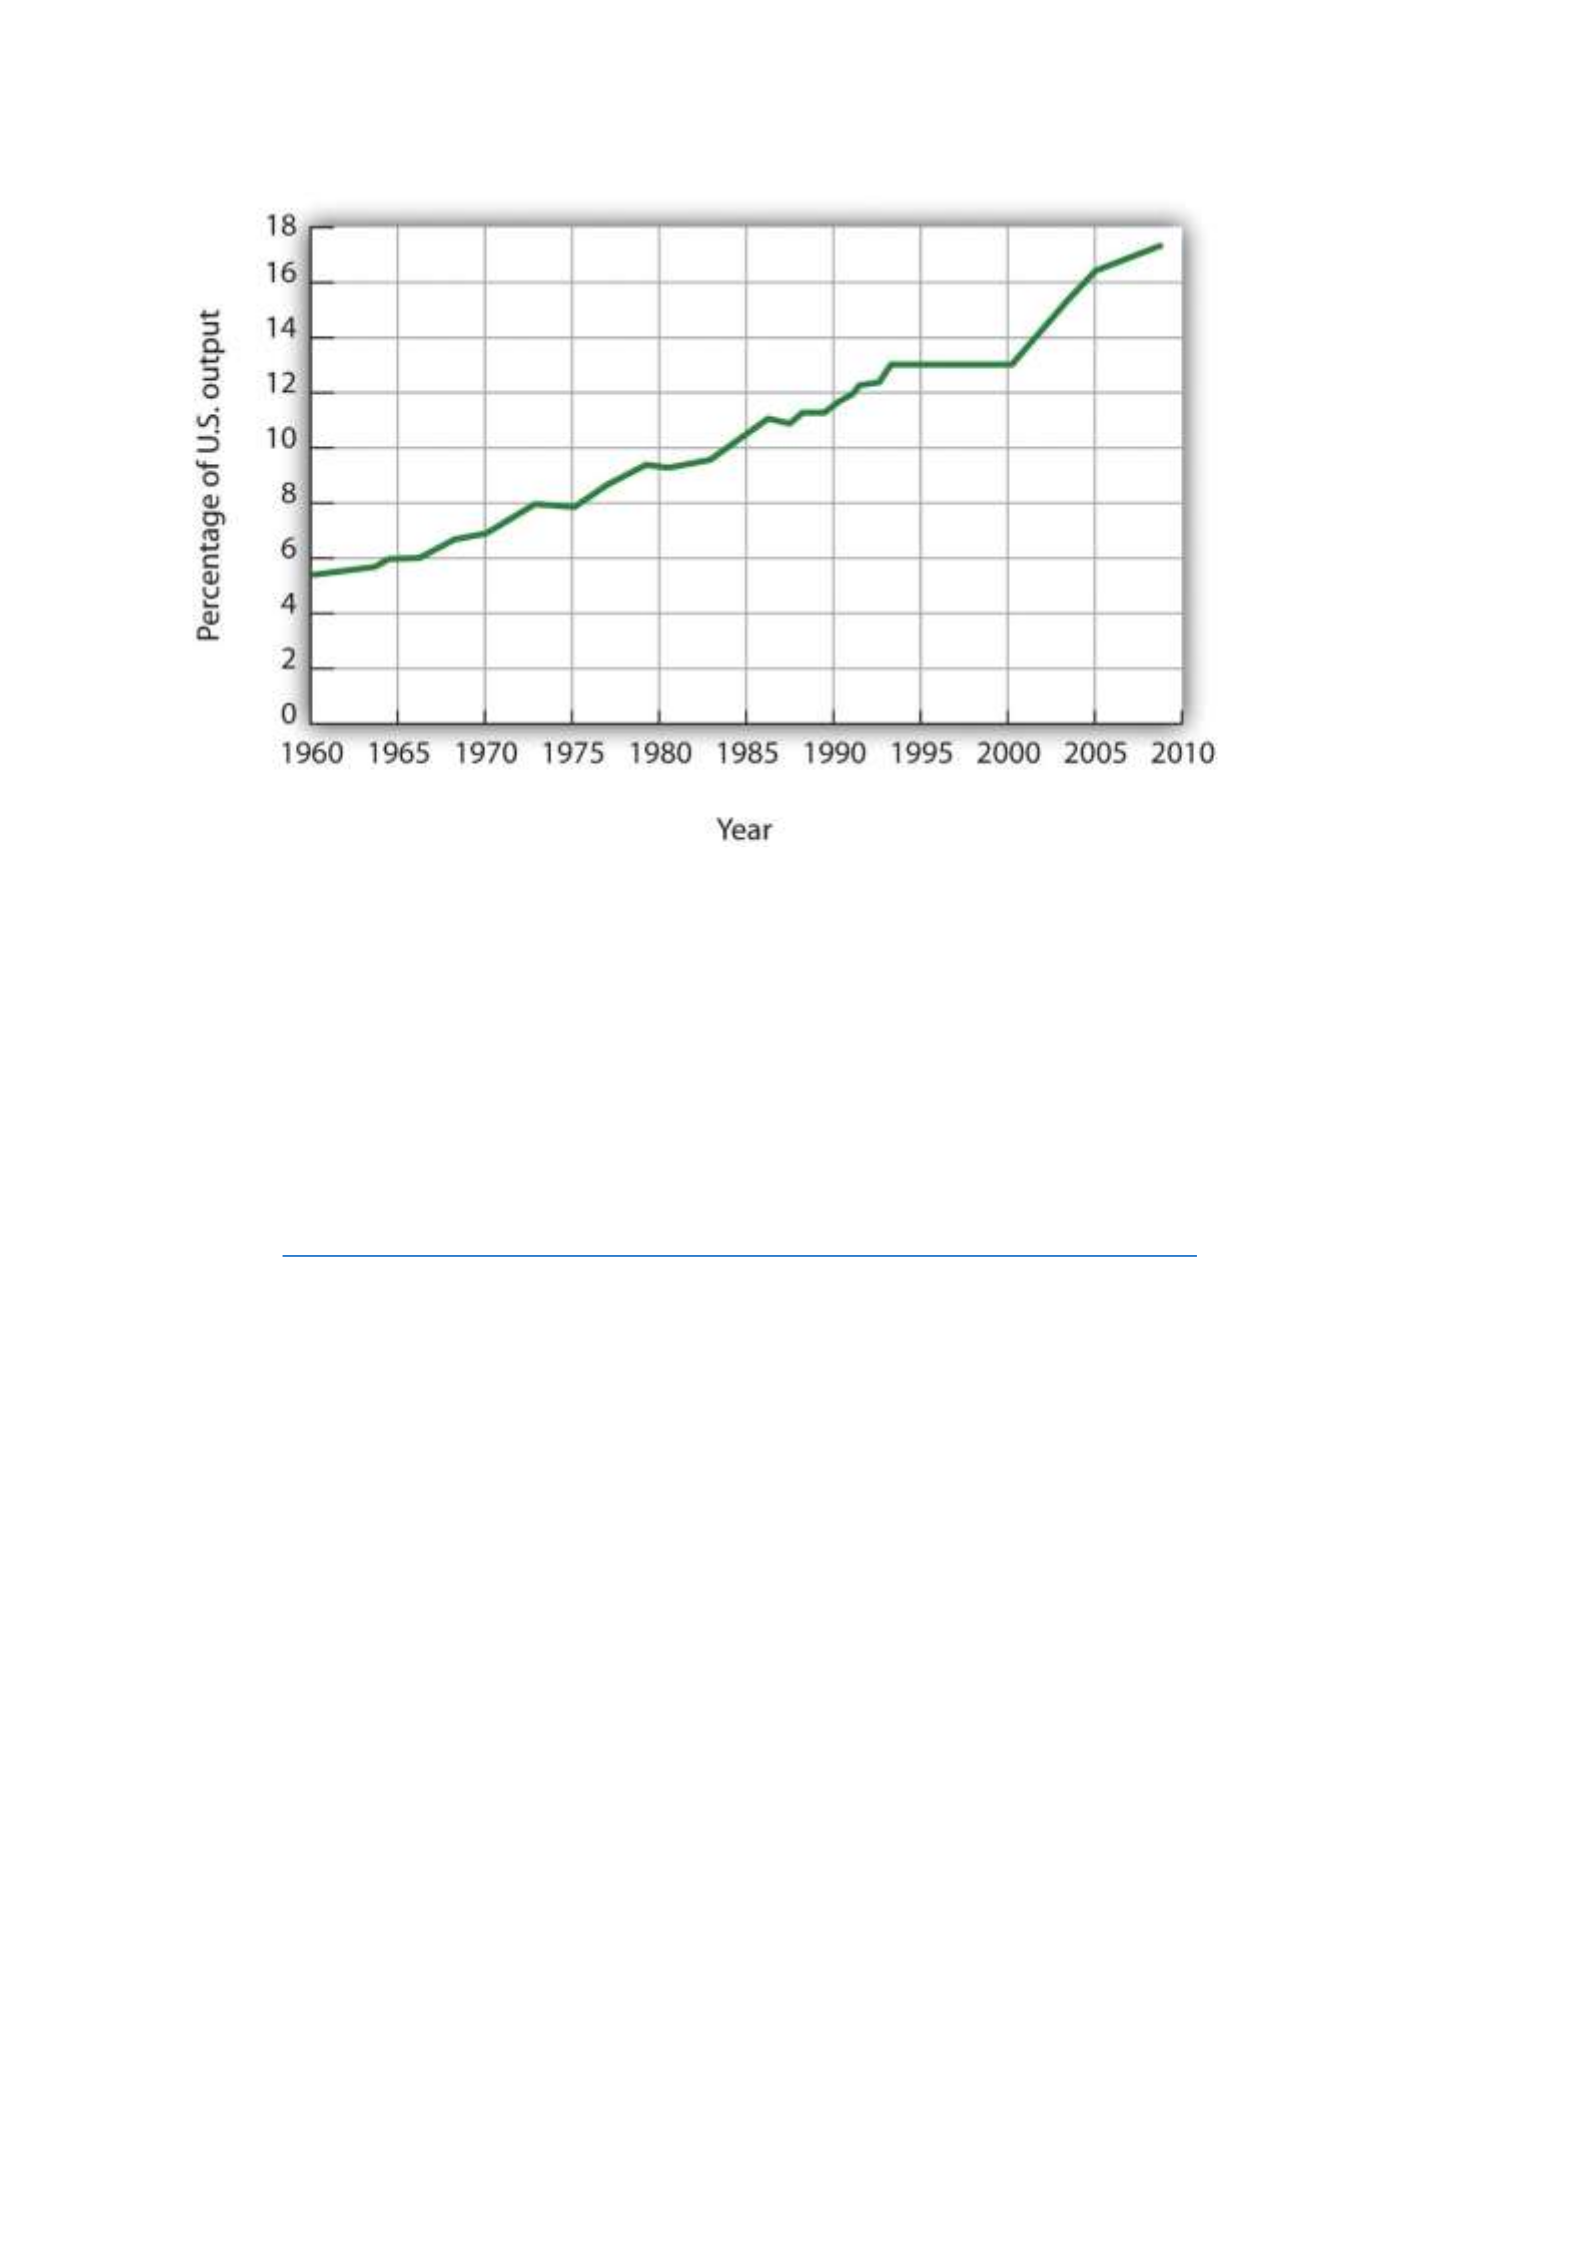
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
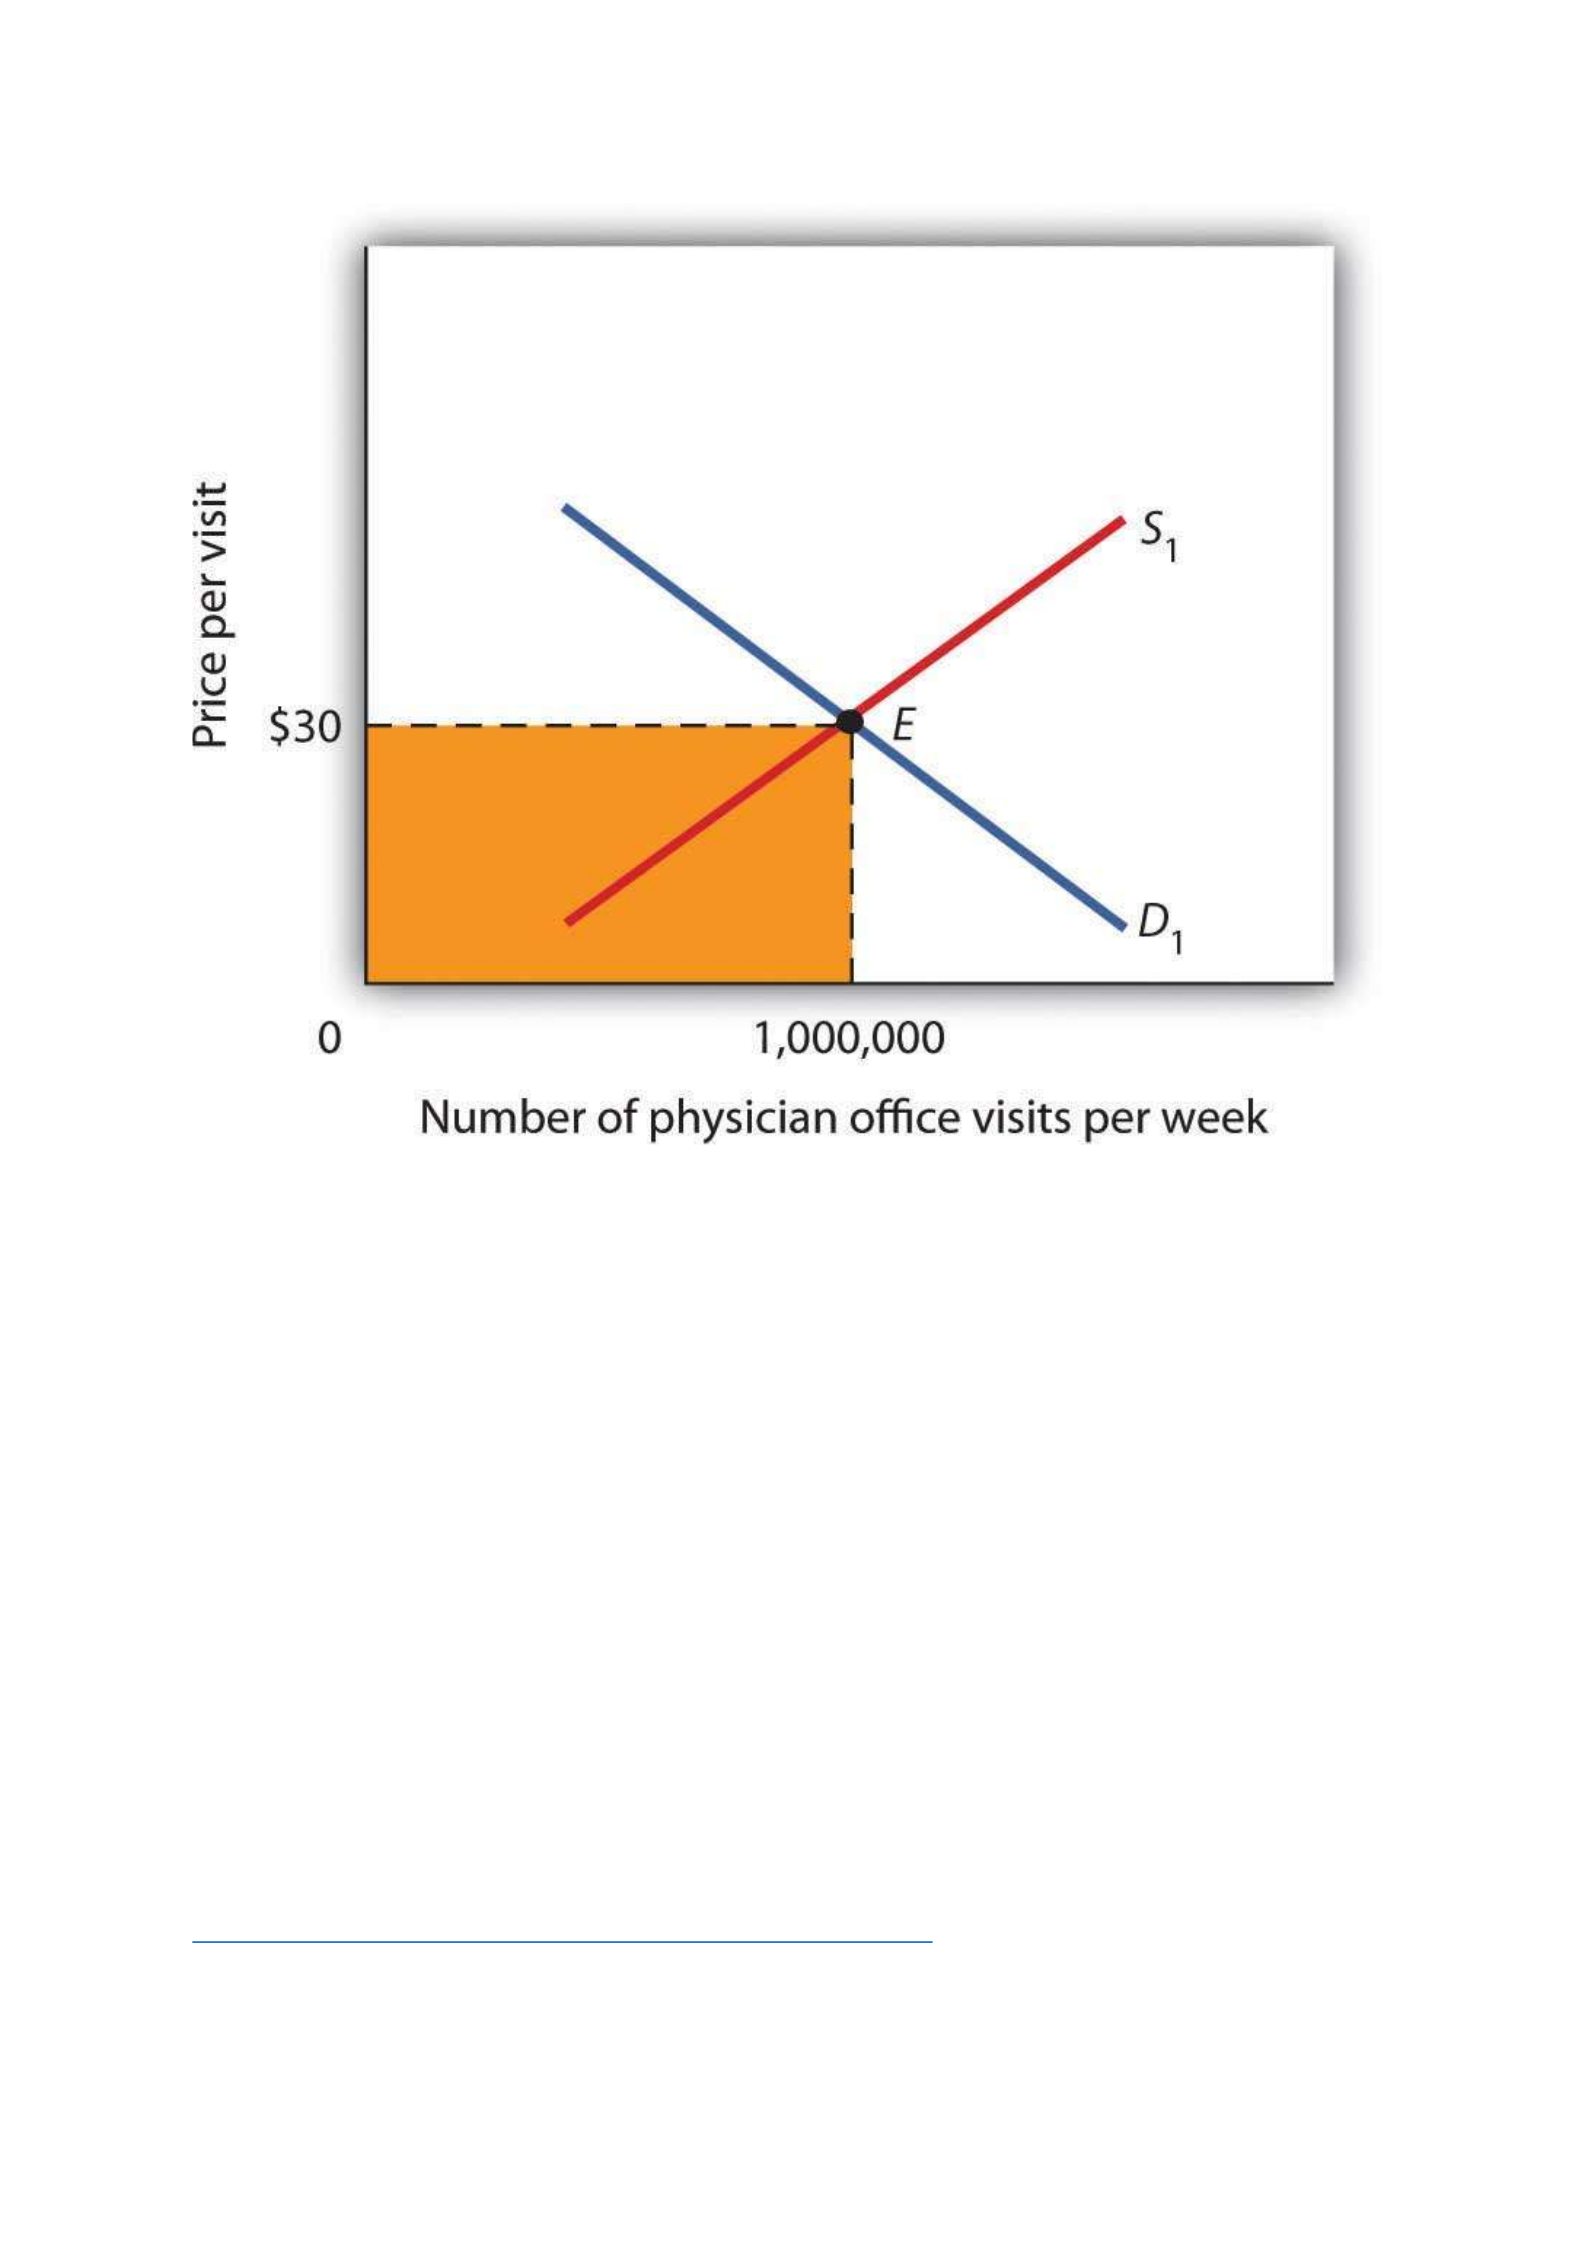
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
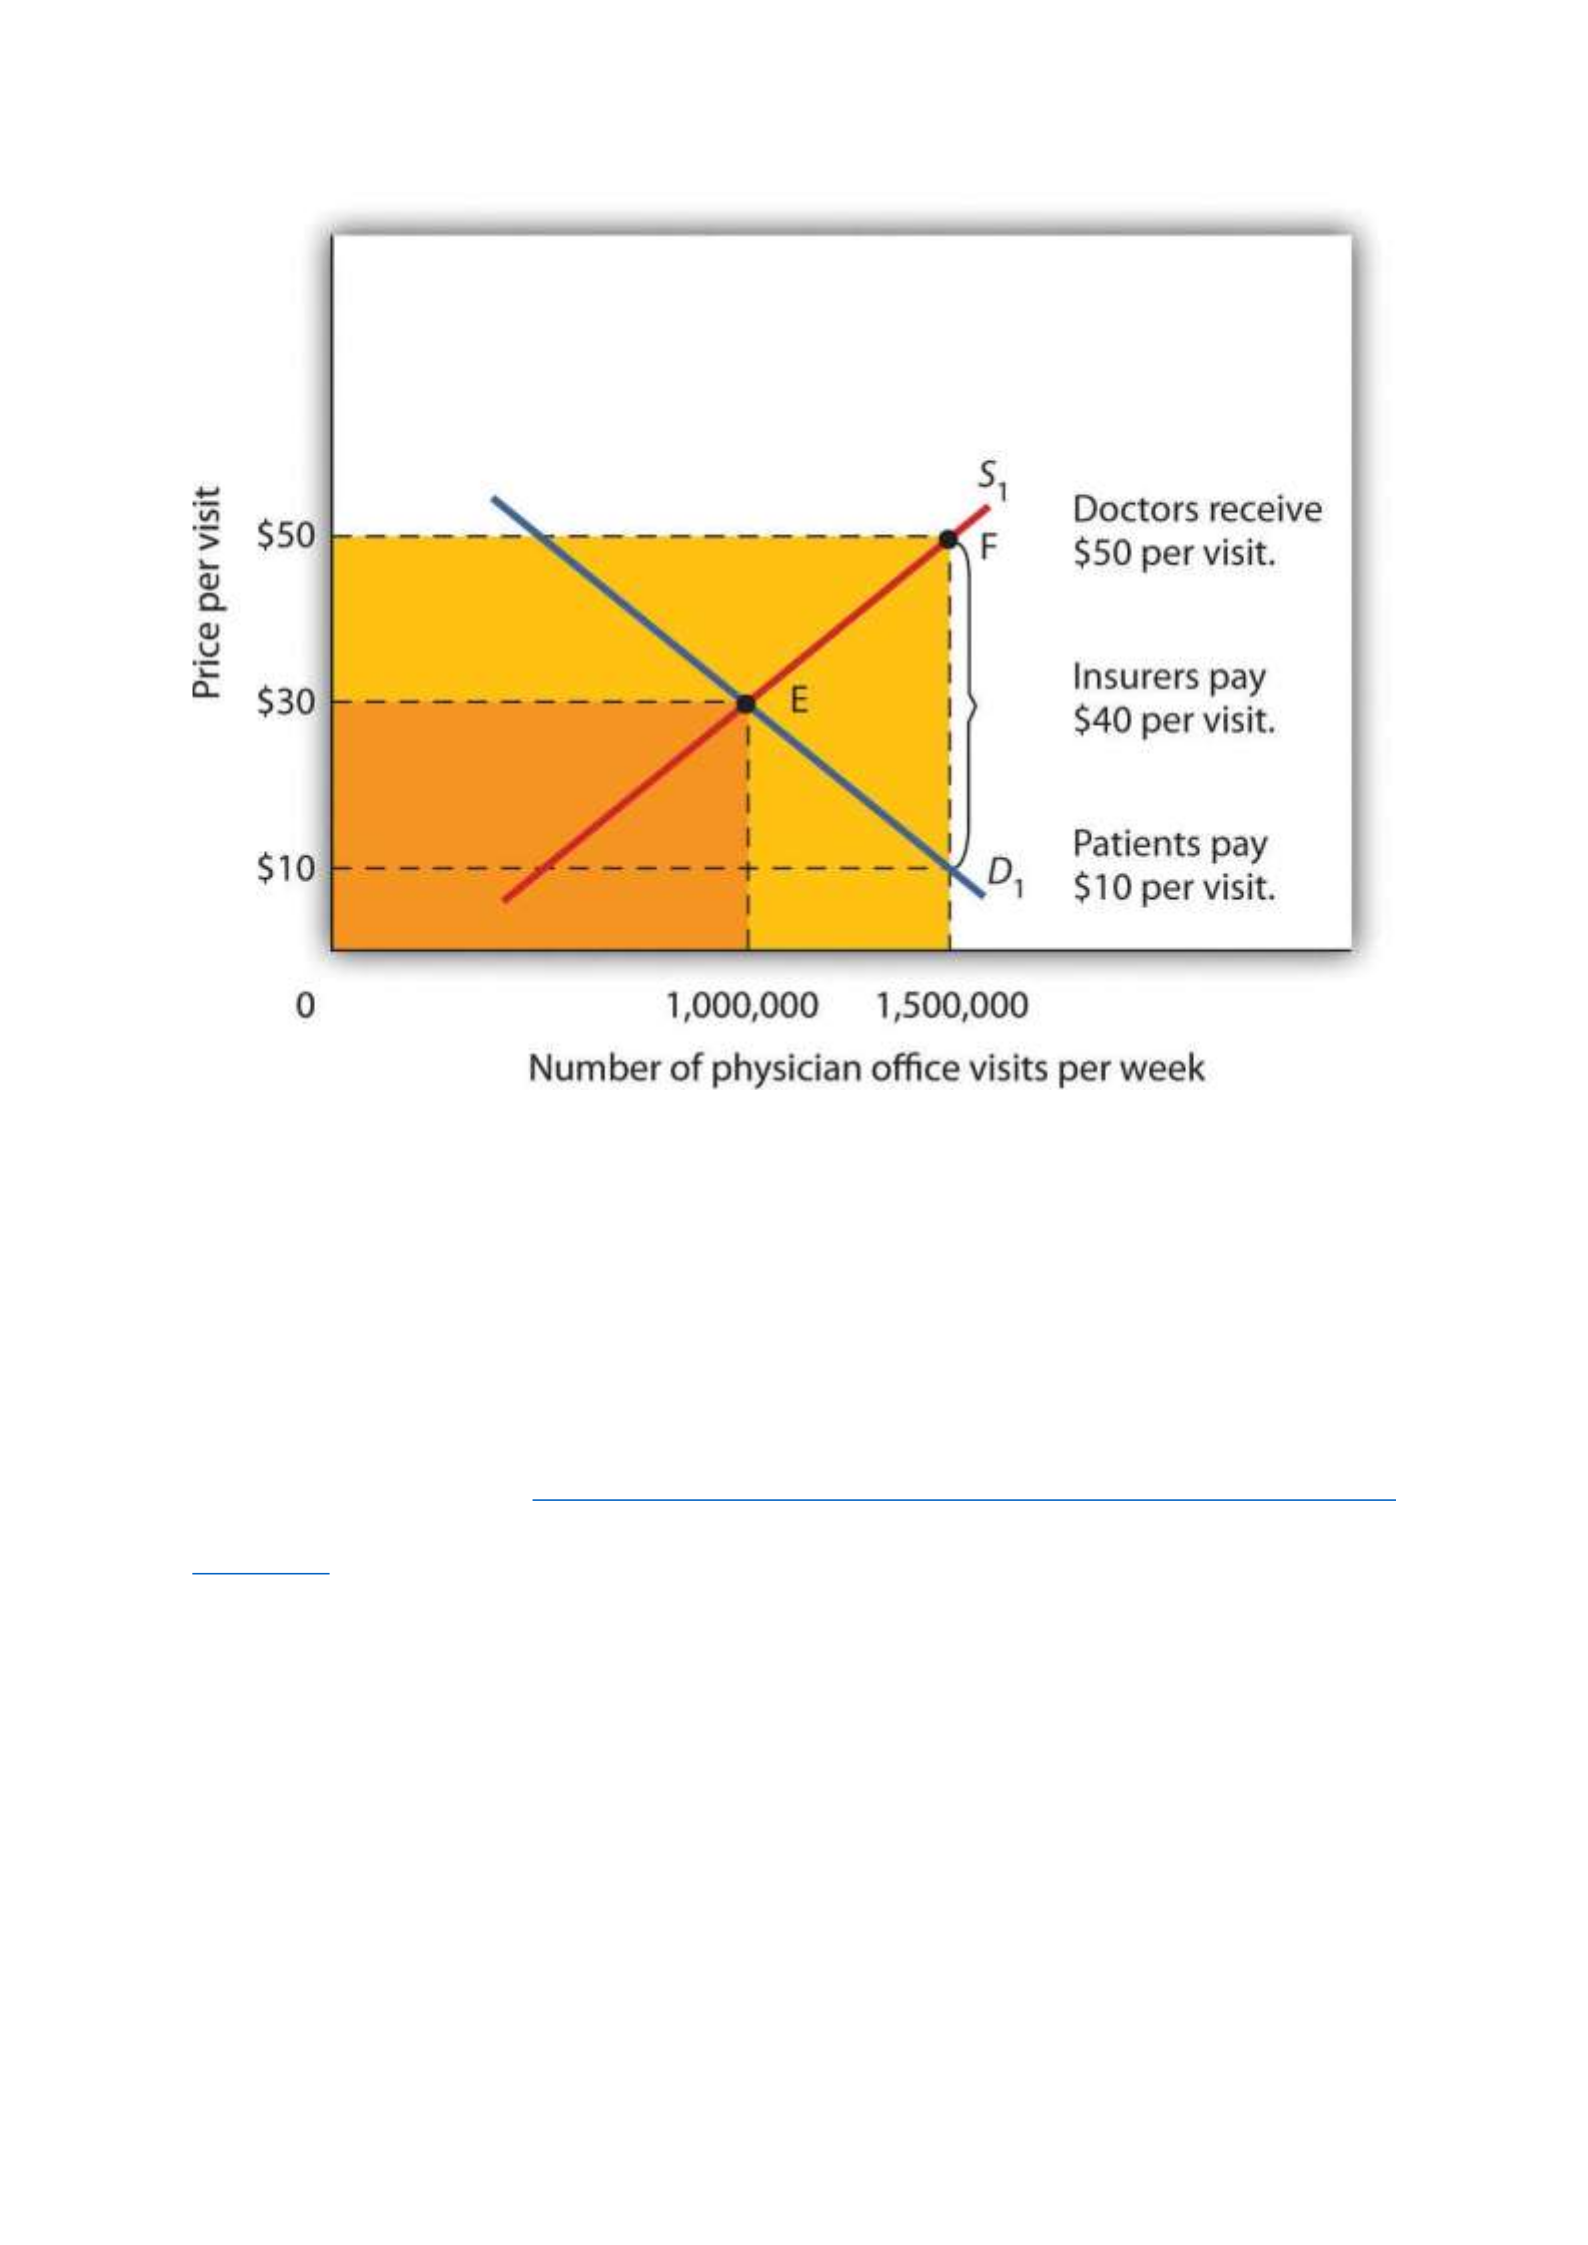
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.
There has been much discussion over the past three decades about the health-care problem in
the United States. Much of this discussion has focused on rising spending for health care. In
this section, we will apply the model of demand and supply to health care to see what we can
learn about some of the reasons behind rising spending in this important sector of the economy.
Figure 4.10 "Health-Care Spending as a Percentage of U.S. Output, 1960–2009" shows the
share of U.S. output devoted to health care since 1960. In 1960, about 5% of total output was
devoted to health care; by 2009 this share had risen to 17.6%. That means that we are devoting
more of our spending to health care and less to other goods and services.
The Affordable Care Act of 2010 dramatically impacted health care services. Among its
provisions is a requirement that individuals purchase health insurance (the so-called individual
mandate). That provision may well result in the entire Act being ruled unconstitutional by the
courts. As this book went to press, the Act was pending before the court system, and a ruling
against it, or at least against parts of it, seemed possible.
The Act requires insurance companies to provide coverage for children on their parent’s
policies up to the age of 26. It also bars health insurance companies from denying coverage
based on pre-existing conditions.
Provisions of the Act are extensive. It applies to virtually every aspect of health care services.
It allows people to acquire health care insurance regardless of pre-existing conditions. It also
allows employers to opt out of providing health insurance and to pay a fee instead.
Figure 4.10 Health-Care Spending as a Percentage of U.S. Output, 1960–2009
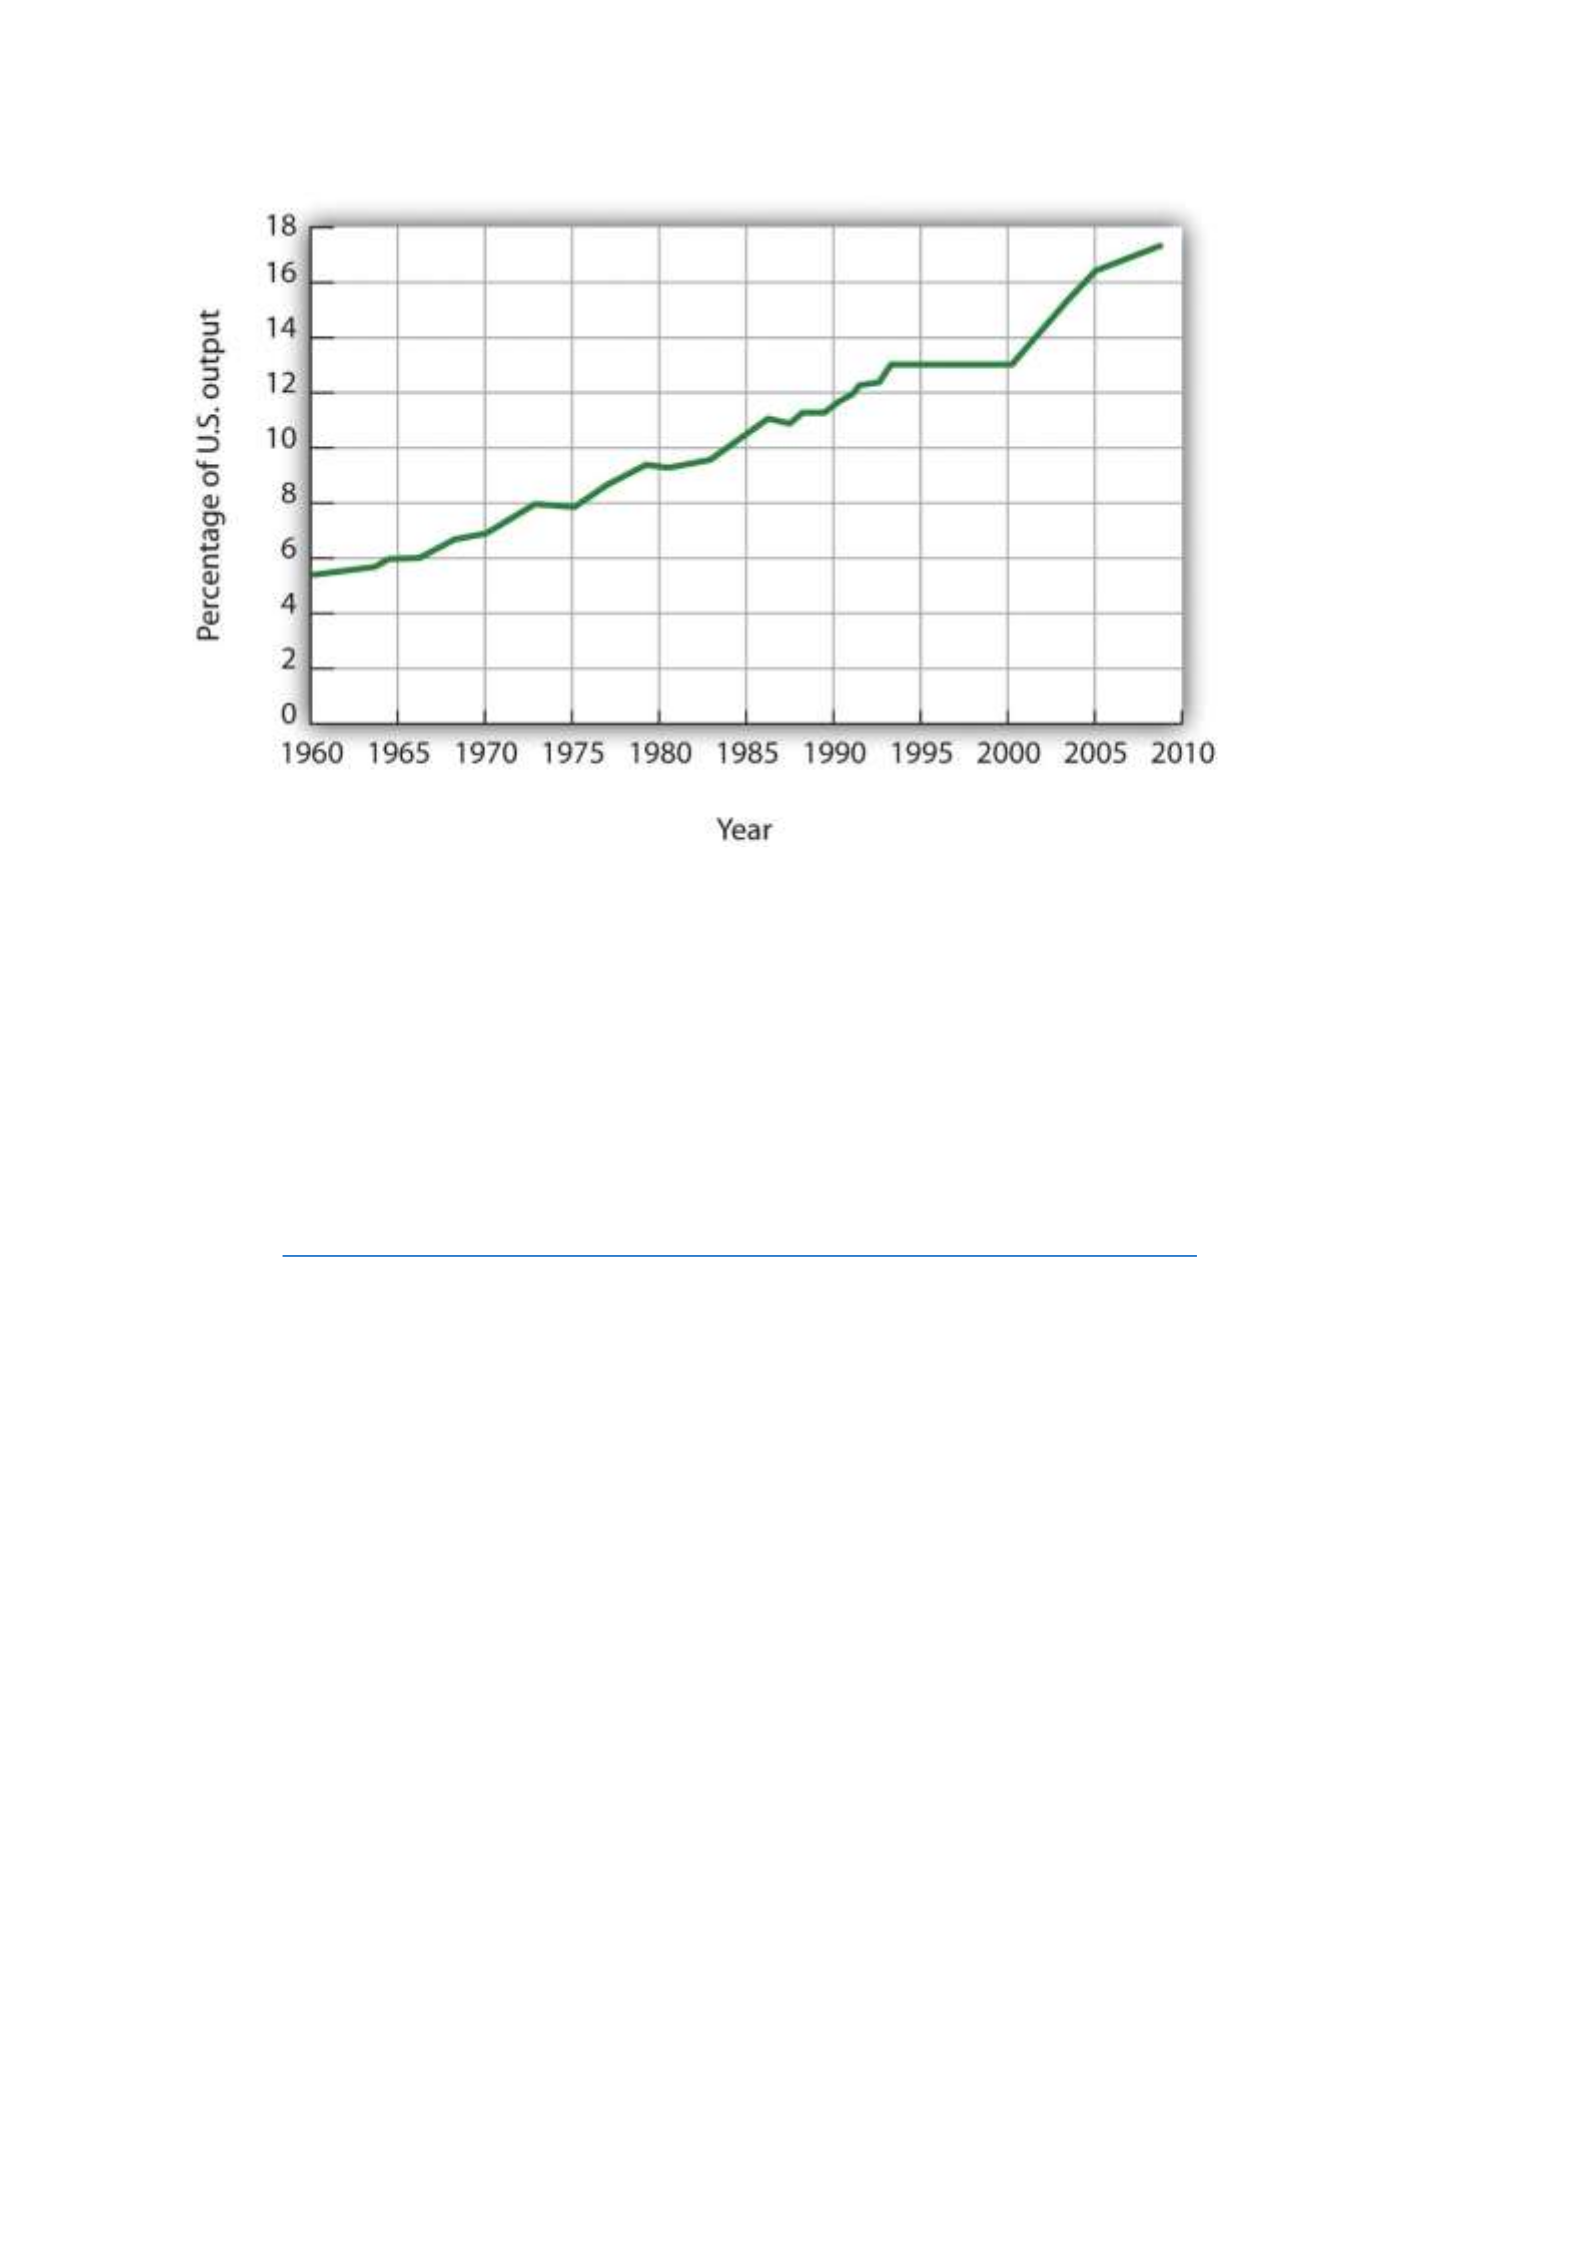
Health care’s share of total U.S. output rose from about 5% in 1960 to 17.6% in 2009.
Data for period 1960–1992 from Health Care Finance Association (which was the predecessor
to the Centers for Medicare and Medicaid Services); Data for period 1993–2009 from Centers
for Medicare and Medicaid Services, Office of the Actuary: National Health Statistics
Group https://www.cms.gov/NationalHealthExpendData/downloads/tables.pdf.
Why were Americans willing to increase their spending on health care so dramatically? The
model of demand and supply gives us part of the answer. As we apply the model to this problem,
we will also gain a better understanding of the role of prices in a market economy.
The Demand and Supply for Health Care
Figure 4.11 Total Spending for Physician Office Visits
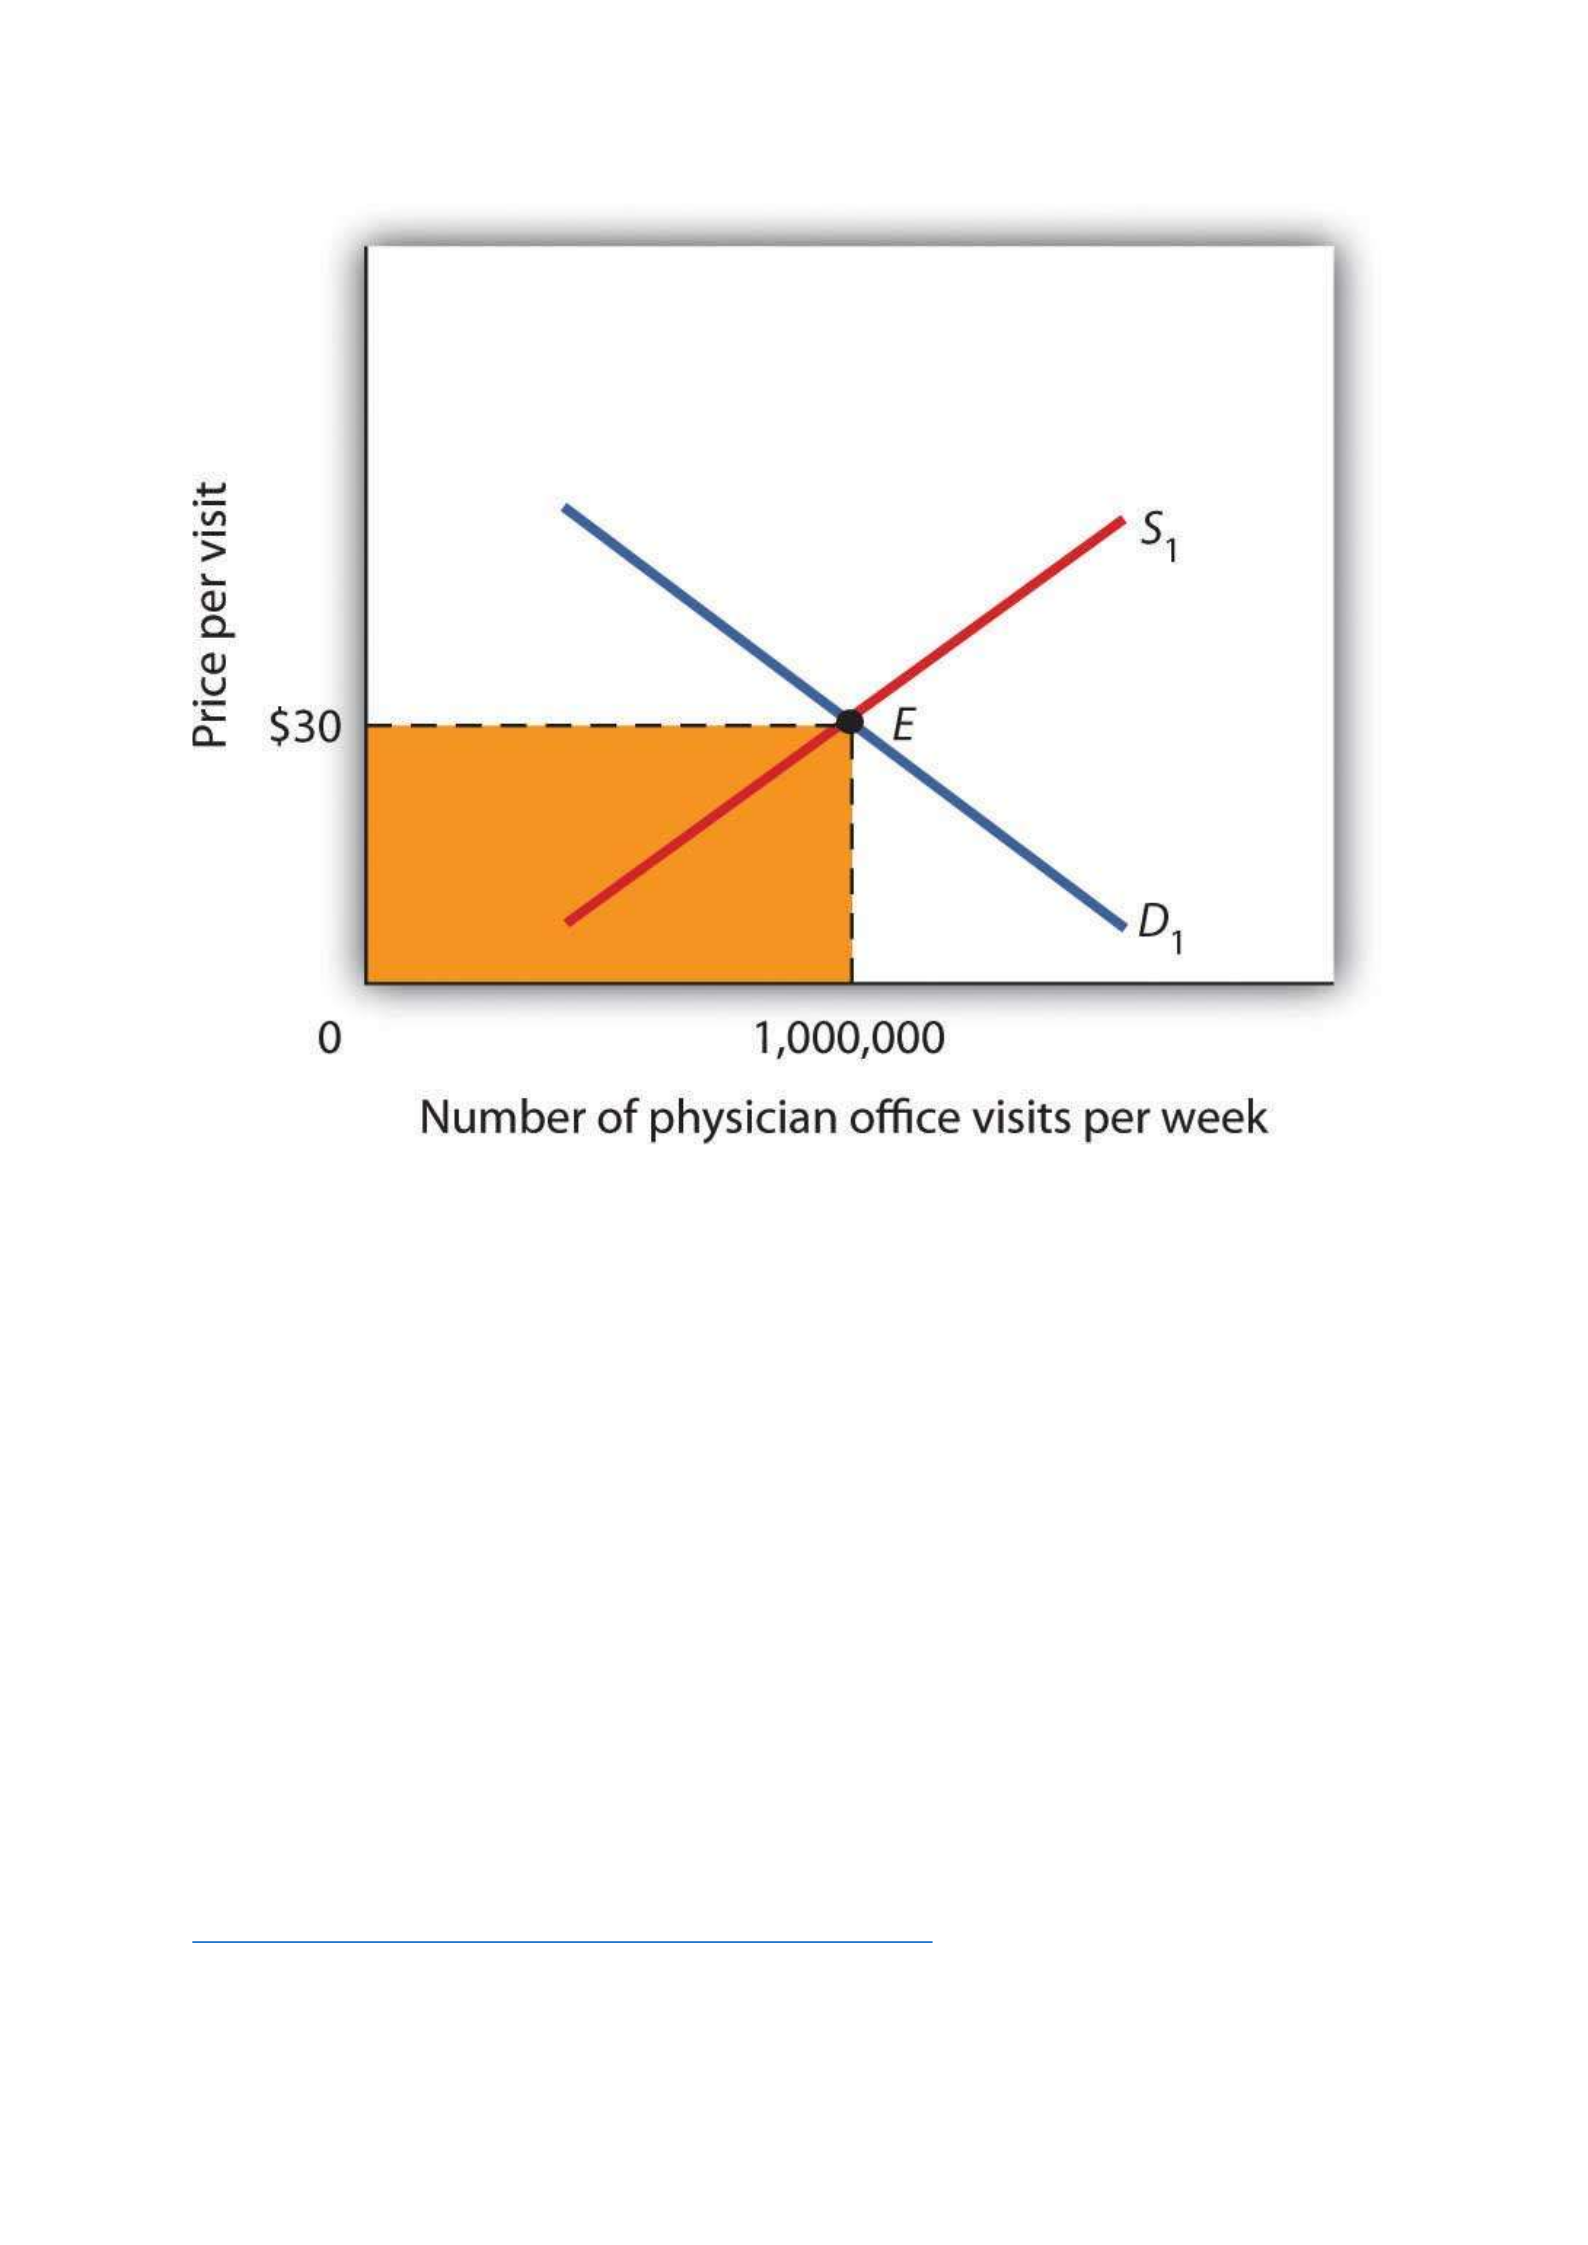
Total spending on physician office visits is $30 per visit multiplied by 1,000,000 visits per week,
which equals $30,000,000. It is the shaded area bounded by price and quantity.
When we speak of “health care,” we are speaking of the entire health-care industry. This
industry produces services ranging from heart transplant operations to therapeutic massages; it
produces goods ranging from X-ray machines to aspirin tablets. Clearly each of these goods
and services is exchanged in a particular market. To assess the market forces affecting health
care, we will focus first on just one of these markets: the market for physician office visits.
When you go to the doctor, you are part of the demand for these visits. Your doctor, by seeing
you, is part of the supply.
Figure 4.11 "Total Spending for Physician Office Visits" shows the market, assuming that it
operates in a fashion similar to other markets. The demand curve D1 and the supply

curve S1 intersect at point E, with an equilibrium price of $30 per office visit. The equilibrium
quantity of office visits per week is 1,000,000.
We can use the demand and supply graph to show total spending, which equals the price per
unit (in this case, $30 per visit) times the quantity consumed (in this case, 1,000,000 visits per
week). Total spending for physician office visits thus equals $30,000,000 per week ($30 times
1,000,000 visits). We show total spending as the area of a rectangle bounded by the price and
the quantity. It is the shaded region in Figure 4.11 "Total Spending for Physician Office Visits".
The picture in Figure 4.11 "Total Spending for Physician Office Visits" misses a crucial feature
of the market. Most people in the United States have health insurance, provided either by
private firms, by private purchases, or by the government. With health insurance, people agree
to pay a fixed amount to the insurer in exchange for the insurer’s agreement to pay for most of
the health-care expenses they incur. While insurance plans differ in their specific provisions,
let us suppose that all individuals have plans that require them to pay $10 for an office visit;
the insurance company will pay the rest.
How will this insurance affect the market for physician office visits? If it costs only $10 for a
visit instead of $30, people will visit their doctors more often. The quantity of office visits
demanded will increase. In Figure 4.12 "Total Spending for Physician Office Visits Covered
by Insurance", this is shown as a movement along the demand curve. Think about your own
choices. When you get a cold, do you go to the doctor? Probably not, if it is a minor cold. But
if you feel like you are dying, or wish you were, you probably head for the doctor. Clearly,
there are lots of colds in between these two extremes. Whether you drag yourself to the doctor
will depend on the severity of your cold and what you will pay for a visit. At a lower price, you
are more likely to go to the doctor; at a higher price, you are less likely to go.

In the case shown, the quantity of office visits rises to 1,500,000 per week. But that suggests a
potential problem. The quantity of visits supplied at a price of $30 per visit was 1,000,000.
According to supply curve S1, it will take a price of $50 per visit to increase the quantity
supplied to 1,500,000 visits (Point F on S1). But consumers—patients—pay only $10.
Insurers make up the difference between the fees doctors receive and the price patients pay. In
our example, insurers pay $40 per visit of insured patients to supplement the $10 that patients
pay. When an agent other than the seller or the buyer pays part of the price of a good or service,
we say that the agent is a third-party payer.
Notice how the presence of a third-party payer affects total spending on office visits. When
people paid for their own visits, and the price equaled $30 per visit, total spending equaled $30
million per week. Now doctors receive $50 per visit and provide 1,500,000 visits per week.
Total spending has risen to $75 million per week ($50 times 1,500,000 visits, shown by the
darkly shaded region plus the lightly shaded region).
Figure 4.12 Total Spending for Physician Office Visits Covered by Insurance
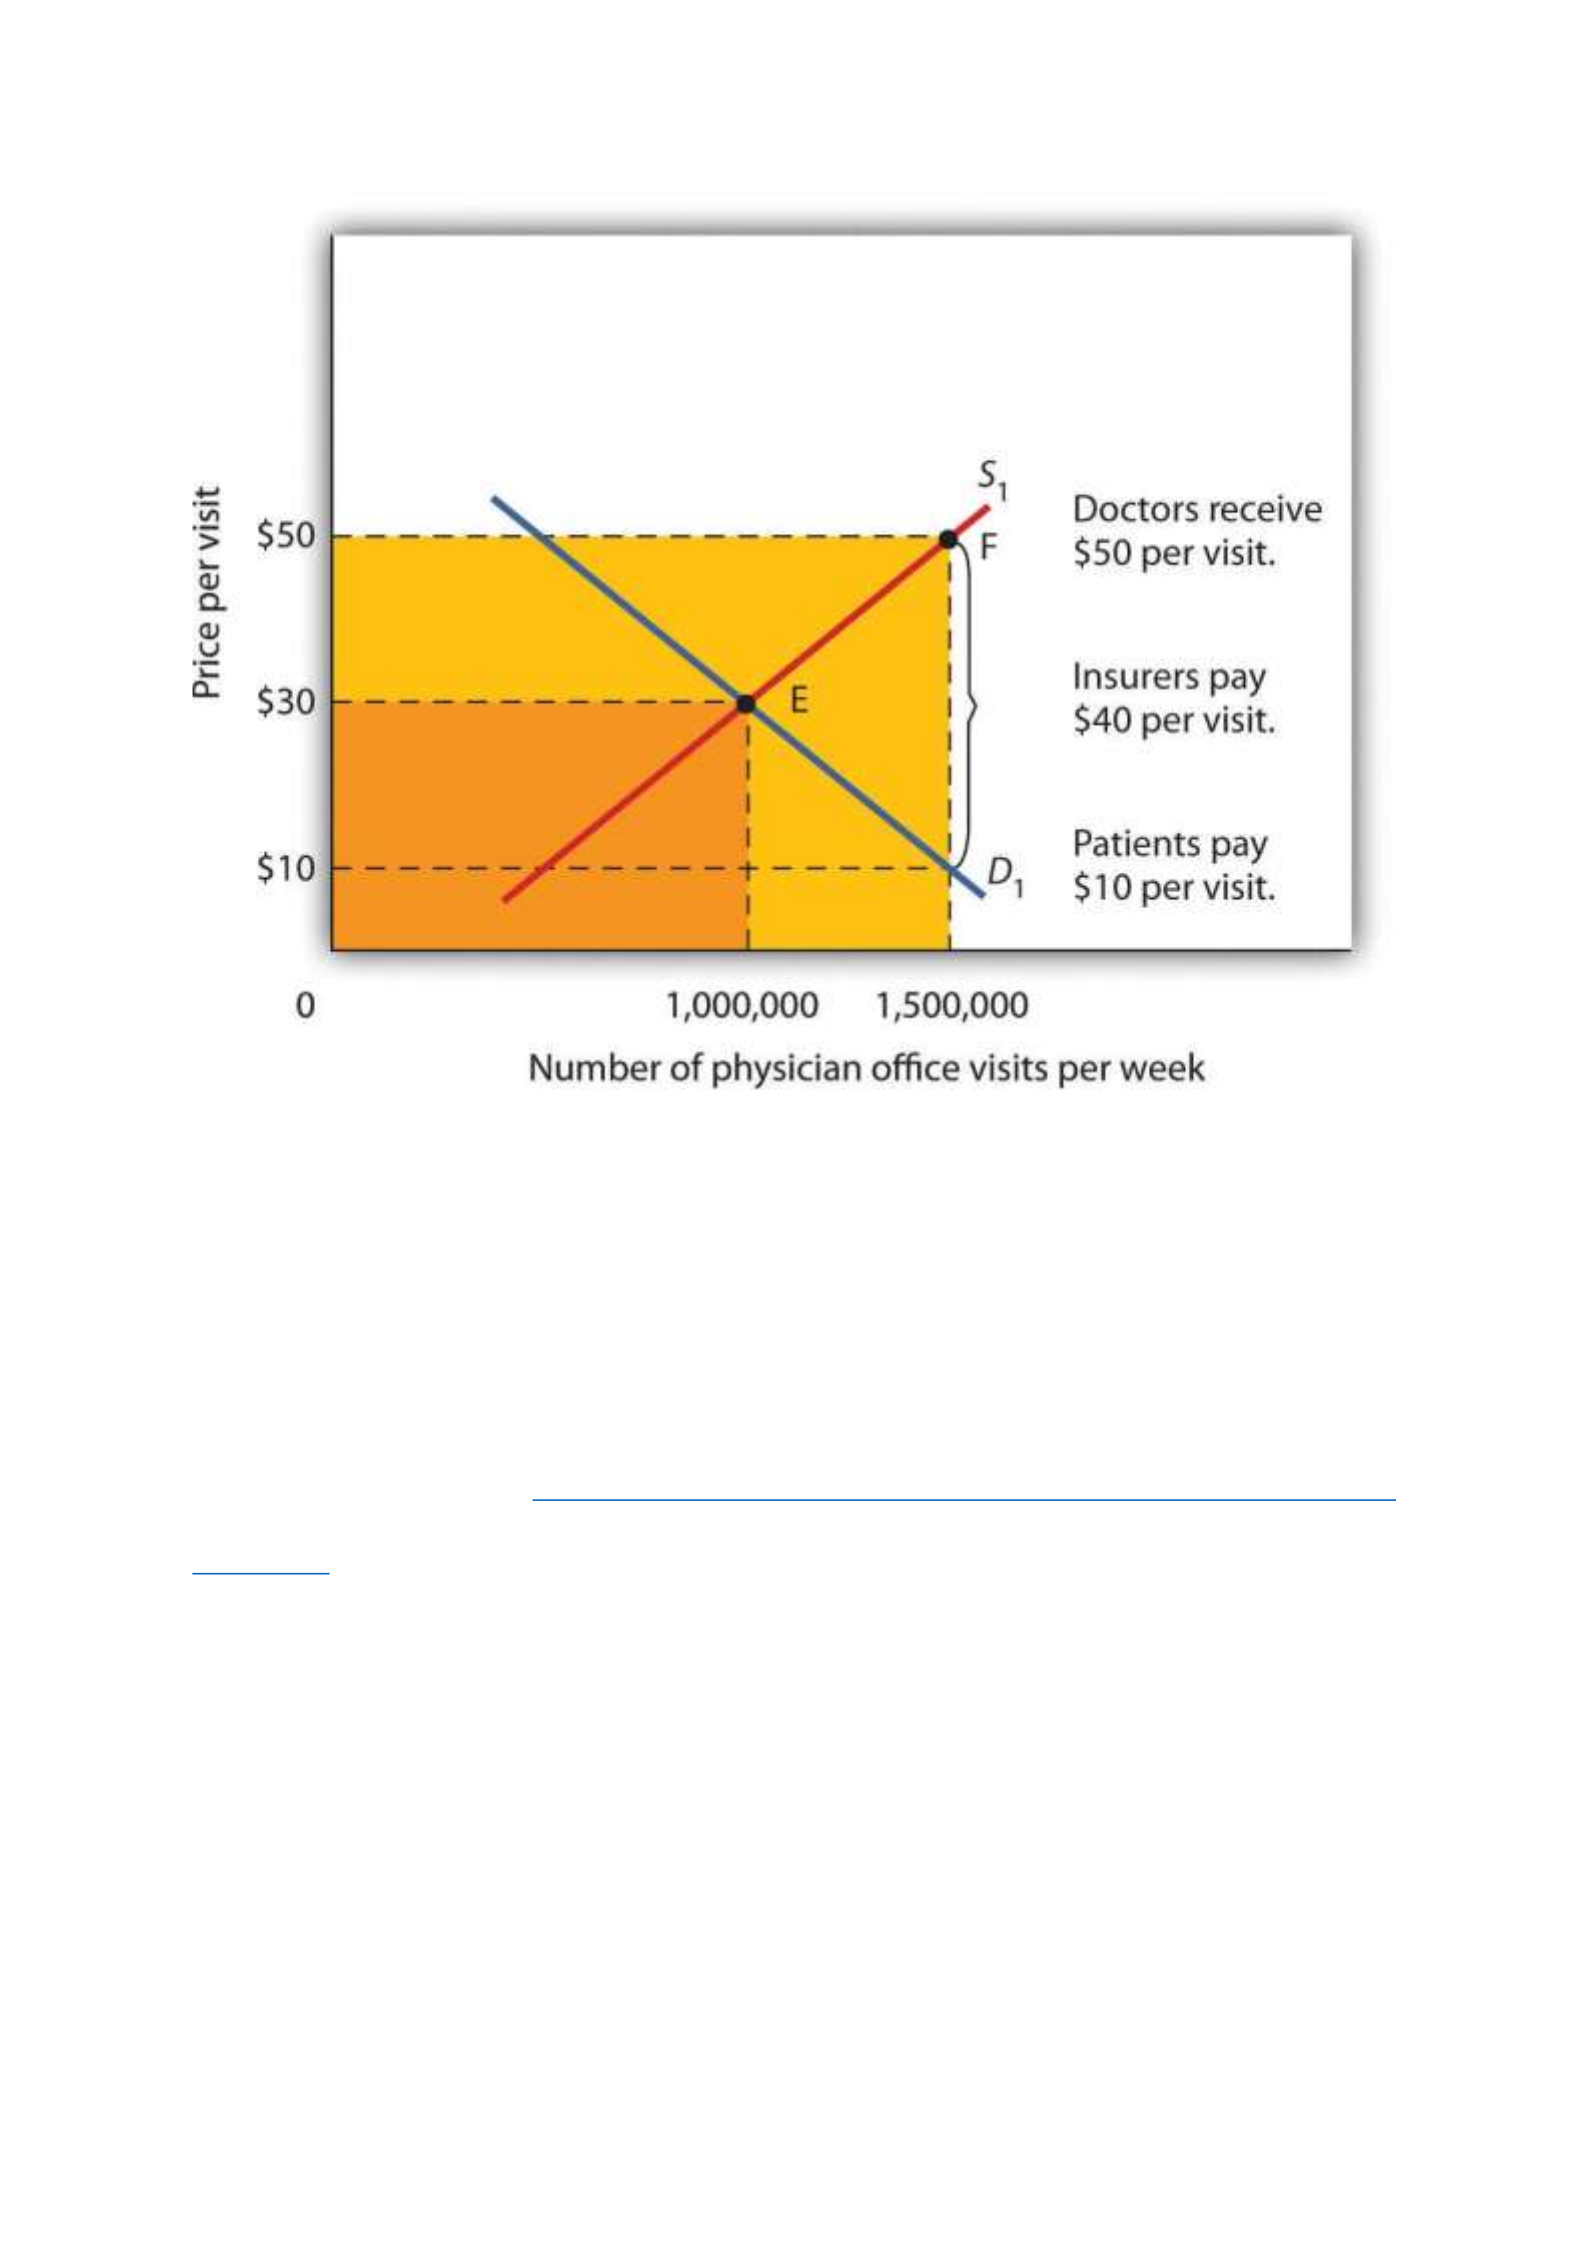
With insurance, the quantity of physician office visits demanded rises to 1,500,000. The supply
curve shows that it takes a price of $50 per visit to increase the quantity supplied to 1,500,000
visits. Patients pay $10 per visit and insurance pays $40 per visit. Total spending rises to
$75,000,000 per week, shown by the darkly shaded region plus the lightly shaded region.
The response described in Figure 4.12 "Total Spending for Physician Office Visits Covered by
Insurance" holds for many different types of goods and services covered by insurance or
otherwise paid for by third-party payers. For example, the availability of scholarships and
subsidized tuition at public and private universities increases the quantity of education
demanded and the total expenditures on higher education. In markets with third-party payers,
an equilibrium is achieved, but it is not at the intersection of the demand and supply curves.
The effect of third-party payers is to decrease the price that consumers directly pay for the
goods and services they consume and to increase the price that suppliers receive. Consumers

use more than they would in the absence of third-party payers, and providers are encouraged
to supply more than they otherwise would. The result is increased total spending.

