



1
Chapter 1: Introduction to the Study
In the United States, educating children is a multidimensional task involving active roles
for many participants, including teachers, parents, government, school-based health service
providers, and the community at large. When some children fail to thrive in an academic
environment, the causes may include the physical and emotional wellbeing of the child, as well
as the interplay of political, economic, and cultural factors. Emotional wellbeing has an impact
on learning and development (Cuellar, 2015; Milovancevic & Jovicic, 2013). A child’s mental
health is linked with interpersonal relationships, social skills, academic motivation, disabilities,
crisis prevention, school safety, and substance abuse (Eklund, Vaillancourt, & Pedley, 2013;
Milovancevic & Jovicic, 2013). Bains (2014) and DuPaul, Reid, Anastopoulos, and Power
(2014) found that one in five adolescents suffer from mental disorders, coupled with many them
living with a sub threshold of emotional stress. Adolescents from low socioeconomic status (SE)
status are predisposed to experience higher poverty rates, learning problems, more frequent drug
abuse, and increased community violence (Cuellar, 2015; Gamble & Lambros, 2014; Subtirelu,
Rincon-Subtirelu, Pickett, & Health, 2014). It was important to investigate the factors that
impact disparities in mental health service use by adolescents. The findings may contribute to
perspectives on the unmet mental health needs of all adolescents. Therefore, exploring the
perceptions of one of the main stakeholders of school-based mental health services (SBMH),
namely school counselors, was imperative.
The purpose of this study was to examine SBMHCs' perspectives about factors affecting
the use of SBMH services by adolescents ages 12 to 17, from a school district in Connecticut.
SBMHCs are school staff whose primary job function is to work with adolescents to ensure they

2
achieve developmental milestones, acquire problem-solving skills, and develop healthy
interpersonal relationships (American School Counselors Association [ASCA], 2015). SBMHCs
work in collaboration with other SBMH professionals, such as psychologists, nurses, social
workers, special education teachers, and others in the school counseling milieu who are the first
responders in identifying a child’s mental health needs. SBMHCs perform different functions,
including mental health assessments, prevention, intervention, and referrals, while focusing on
how mental health affects learning and ensures academic success for adolescents with identified
behavior problems (ASCA, 2015). SBMHCs' role functions may help school administrators,
school staff, and parents increase collaborative efforts to help at-risk adolescents with unmet
mental health needs.
SBMHCs' job descriptions require them to spend 500 to 1,700 hours in supervised
training, in addition to academic qualifications, before entering direct professional contact with
adolescents (ASCA, 2015). School settings are fertile grounds for helping adolescents develop
skills, knowledge, and attitude vital for future life successes and maintaining healthy habits. The
investigation of SBMHCs' perspectives may lead to the discovery of strategies to connect and
build relationships with adolescents that can affect their decision to use SBMH services.
SBMHCs’ perspectives rarely are included when schools consider how to help
adolescents presenting with mental health issues (Collins, 2014). Including the perspectives of all
stakeholders in adolescent mental health care could help increase adolescent use of mental health
services (Gamble & Lambros, 2014). Lewis, McCallister, and Browning (2015) found that
collaborative efforts among schools, families, and SBMH service professionals promoted
improved academic and mental health outcomes. Milovancevic and Jovicic (2013) posited that

3
improving adolescents’ mental health requires the establishment of partnerships and defining
roles among schools and school management. It is imperative that the perspectives of SBMHCs
are included in the development of programs that address the mental health needs of adolescents.
Despite previous research on school-based health services, SBMH services remain an
inadequately researched sector of the United States health delivery system (Williams, Sands,
Elsom, & Prematunga, 2015; Wrigley, 2015). The goal of previous SBMH researchers was to
measure the effectiveness of SBMH services and evaluate the effects of mental health on
adolescent academic achievement. Researchers have conducted minimal in-depth examinations
of SBMH service use by adolescents from the perspective of SBMH professionals. SBMHCs’
perceptions of factors affecting SBMH service use by adolescents are considerations when
responding to student demographic change and the need to eliminate differences in service use
(Adams, 2015). In addition, SBMHCs’ perceptions may reveal new information leading to ways
to meet the needs of adolescents.
SBMH clinics are the first point of contact for adolescents’ mental health care needs. As
of 2014, there were 1,900 school-based health programs across the United States (National
Education Statistics, 2015). SBMH services include assessment, prevention, intervention, and
referral services delivered to children in a school setting (ASCA, 2015). Although recognized as
the primary provider of mental health services for children and adolescents (National Association
of School Psychologists [NASP], 2015; Weist et al., 2014), SBMH services remain a topic of
interest and further exploration.
The dissemination of SBMHCs ‘perceptions study findings may lead to several positive
social changes. For example, the study findings may help school administrators target and

4
develop programs to reduce adverse effects of mental health on academic performances of
adolescents who may not use services. The findings may also reduce the economic costs of
providing special education and lower incarceration rates for adolescents with identifiable mental
health issues. Understanding why some adolescents seek help and others do not, from the
perception of SBMHCs, could help school district administrators and educators gain insight into
why disparities in service use exist within different groups of adolescents. New information
might also bolster current SBMH service protocols and provide opportunities to adapt policies to
meet the needs of diverse student populations. SBMHCs’ perceptions on mental health support
for adolescents in education may illuminate the kinds of collaborative efforts required to address
adolescents’ unmet mental health needs.
Background
School districts in the United States experience constraints due to regulatory
requirements for promoting adolescents’ academic achievement, stakeholders’ demands for
technology, and state budget deficits affecting school funding (Jones, Mundy, & Perez, 2014;
Topper & Lancaster, 2013; Yettick, Baker, Wickersham, & Hupfeld, 2014). Educators must
balance educating adolescents while ensuring that their emotional wellbeing is conducive for
achieving developmental milestones (Jones et al., 2014). The relationship between academic
performance, environment, and life trajectory is evident in some United States schools, where
adolescents continue to endure the negative consequences of mental health disorders (Carlson &
Kees, 2013; NASP, 2015). Children with untreated problem behaviors experience barriers to
their learning and are more likely to use services in school settings than in other formal settings
(Bear, Finer, Guo, & Lau, 2014). Research conducted on the perspectives of SBMH service

5
stakeholders about adolescents’ mental health services could deepen the understanding of the
factors that affect the use of services as well as how these variables interact (Carlson & Kees,
2013). It is important to address adolescents’ mental health care needs to improve their ability to
learn and achieve academic success. The prevailing burden of mental disorders among
adolescents is a source of concern for all.
Bains (2014) and Powers, Wegmann, Blackman, and Swick (2014) and Repie (2005)
found that SBMH services are an ongoing area of national concern. Only 20- 36% of United
States adolescents who need help receive treatments (Bains & Diallo, 2016; Bear & Finer, 2014).
Approximately 2.2 million adolescents between the ages of 12 to17 reported having a major
depressive episode within the past 12 months, and 60% of them received no treatment (ASCA,
2015). The Centers for Disease Control and Prevention (CDC, 2015) showed that adolescents’
mental health disorders are prevalent in the United States and argued that these disorders are an
aberration in the normal cognitive, social, and emotional development of the child. The annual
cost of mental health issues by U.S. adolescents was $247 billion and between 13, and 20% of
U.S. children experience mental health disorders each year (CDC, 2015). Suicide, an acute sign
of the interaction of mental illness with other factors, was the leading cause of death for
adolescents aged 12-17 in 2010 (CDC, 2015).
A rationale for this study was the prevalence of adolescents ‘mental disorders, and the
lack of current literature focusing on first responders such as SBMHCs. Adolescents from low
socioeconomic areas experience limited use of quality mental health services and have higher
levels of unmet mental health needs than their counterparts have (Gamble & Lambros, 2014;

6
Lindsey, Chambers, Pohle, Beall, & Lucksted, 2013). Understanding why adolescents from a
school district in Connecticut underuse SBMH services was imperative.
Several factors account for disparities in SBMH service use by adolescents. For example,
both Black adolescents and non-Black adolescents abstain from using the available services due
to perceptions of mental health services and social norms that inhibit them from seeking help
(Lindsey et al., 2013). Bogart et al. (2013) examined the association between perceived
discrimination and racial/ethnic disparities. Discrimination results in stress responses and poor
behavior choices that have negative consequences on the individual’s ability to maintain physical
and mental health (Bogart et al., 2013). Urban adolescents experience greater burden of unmet
mental health needs that affects their academic performance.
By investigating factors that affect disparities in SBMH services use by adolescents, I
addressed a gap in the literature on SBMHCs’ perceptions. SBMHCs are vital to the academic
and emotional growth of adolescents. The invaluable role and input of SBMHCs is key to
encouraging adolescents to use SBMH services (Batterham, 2015). The goal of the NASP (2015)
is to increase awareness and improve SBMH services. SBMHCs’ perceptions could contribute to
initiating new policy by providing school administrators with information that may lead to
interventions to address adolescents’ unmet mental health needs.
Problem Statement
SBMH services provide care for children and adolescents with varying emotional and
psychological needs that negatively affect their academic success. Bains (2014); Bowers,
Manion, Papadopoulos, and Gauvreau (2013); and Brock (2015) demonstrated that unmet mental
health needs are a problem among a significant number of adolescents with identifiable mental

7
disorders who could benefit from SBMH services. The SBMHCs’ perspectives are not included
when identifying factors that affect adolescents’ use of SBMH services. Repie (2005)
investigated the perceptions of special education teachers, school counselors, and school
psychologists and suggested that appropriate school-based mental health services should include
balanced functions and proactive measures that lead to greater efficiency.
Adolescents from a school district in Connecticut underuse SBMH services. Yet, the
perceptions of SBMHCs regarding why adolescents are not using the services appear to be
unknown. Perspectives of SBMHCs are a link toward planning and developing evidence-based
programs that may increase adolescents’ use of SBMH services. When adolescents do not
receive adequate and appropriate interventions early in life to remediate mental health disorders,
they grow to face negative life outcomes (Adams, 2015; Flanagan, Farina, & Davidson, 2015;
Furlong, 2015; Kilgus, Reinke, & Jimerson, 2015; Weistet al., 2014). The perceptions of
SBMHCs are elements to addressing the unmet mental health needs of adolescents.
SBMHCs are at the forefront of providing adolescents with preventative services that
circumvent academic failures and underachievement. Adams (2015), Flanagan et al. (2015),
Furlong (2015), Kilgus et al., (2015), Lindsey et al., (2013), and Weistet et al. (2014) indicated
that mental illness affects one in five adolescents in U.S. schools, and only 20% of adolescents
who are diagnosed with emotional and psychological issues are receiving treatment. The rate of
adolescents’ unmet mental health needs is multifaceted because few adolescents use SBMH
services, and many with mental health needs remain unidentified until they reach adulthood.
According to the CDC (2015), 6.8% of children between ages 3 and 17 were diagnosed
with attention-deficit/hyperactivity disorder, 3.5% with behavioral disorders, 3.0% with anxiety,

8
and 2.1% with depression. Substance use disorder for adolescents’ ages 12- to 17-years-old
affected 4.7% for illicit drugs, and 4.2% for alcohol (CDC, 2015). The prevalence of suicide by
adolescents ages 10 to19 was 4.5% per 100,000 persons (CDC, 2015). Mental disorders among
children and adolescents aged 5 to 17 in the State of Connecticut exceeded respiratory disorders
and all other illnesses resulting in hospital admissions (Connecticut Department of Public Health,
2014). The burden of adolescents’ unmet mental health needs has potential long-term negative
social and economic implications for the United States. Understanding why a significant number
of pupils do not seek service is essential to identifying factors affecting service use.
Adolescence is a crucial period in an individual’s lifespan, and it is the most appropriate
time to address the 70% of mental health disorders that emerge before age 18 (Flanagan et al.,
2015). If the mental health needs of adolescents go unmet during this critical time, there is an
increased risk of the decline in student learning, development of interpersonal relationships, and
the pursuit of future life ambitions (NASP, 2015). Only 20% of adolescents with identifiable
mental health needs use services and one-quarter of them do not use services or are undiagnosed
(Bains, 2014; Bear & Finer, 2014; DuPaul et al., 2014). Understanding the factors that affect
disparities in SBMH services use is vital to the future of a school district in Connecticut, in its
effort to plan and develop improved SMBH programs. SBMHCs and their viewpoints are critical
to addressing the unmet mental health needs of adolescents. Incorporating their perspectives may
lead to improved services, resulting in better outcomes for the adolescents.
Purpose of the Study
The purpose of this descriptive, phenomenological study was to examine the perceptions
of SBMHCs about factors affecting the use of SBMH services by adolescents from a school

9
district in Connecticut. Data collection involved the use of face-to-face, semi structur
ed
interviews of 15 SBMHCs. NVivo software was used to help organize, code, and analyze data.
Research Questions
The research questions guiding the purpose of this study were as follows:
RQ1: What do SBMHCs perceive as factors that may affect the use of SBMH services by
adolescents from a school district in Connecticut, United States?
RQ2: What do SBMHCs perceive as barriers meeting the mental health needs of
adolescents from a school district in Connecticut, United States?
Theoretical Framework
The theoretical base for the exploration of SBMH services professionals’ perceptions was
Mechanic’s (1978) theory of help seeking. Mechanic’s framework outlines 10 interrelated
constructs that include stages of illness, assessment of symptoms, its impact on other aspects of
life, frequency, capacity to endure, available information, culture, perceptual needs, the priority
of needs, interpretation of symptoms, and resources availability for understanding determinants
of help-seeking and service use. Mechanic’s theory, as described by Lindsey et al. (2013), was
appropriate for this study because it provided a perspective for understanding help-seeking
behaviors of adolescents. Researchers use the help-seeking model because it combines elements
of constructs contained in the health belief model (Lindsey et al., 2013). The help-seeking model
highlights constructs dealing with such factors as an individual’s attitude towards using mental
health care services, decisions an individual makes while weighing the pros and cons of using
mental health services, and normative pressure to use mental health services (Lindsey et al.,

10
2013). I will use this framework to uncover the unknown reasons that adolescents fail to use
SBMH services.
Nature of Study
The employment of a qualitative approach for this study helped to facilitate a deeper
explanation and understanding of the significance of SBMH services professionals’ perspectives.
Kelly, Pastore, Hodge, and Seifried (2015) and Yilmaz (2013) noted that qualitative research
techniques offer the researcher guidance to focus on how and why phenomena occur. The
emphasis on how and why enabled the collection of rich and detailed information necessary to
provide an understanding of the perspectives of SBMHCs about factors that may affect
adolescents’ use of services. In addition, the use of a qualitative approach with a descriptive
aspect of phenomenology allowed for an in-depth examination of SBMHCs’ perceptions of
factors that may affect adolescents’ use of services.
Bains (2014), Costello (2015), DuPaul et al. (2014), and Milovanceive and Jovicic (2013)
found that the prevalence of mental disorders in the aforementioned age category is 69% higher
than that for children aged 6 to 11. One in five adolescents experience symptoms of mental
illness and of those identified with mental health issues, only 15-20% receive services (Costello,
2015). Adolescents from low SE urban areas experience the highest proportion of risk factors for
learning-related behavioral problems than their counterparts from high SE areas (Morgan,
Farkas, Hillemeier, & Maczuga, 2009).
I chose to study this group because of my professional role as a family therapist and
former member of the integrated service system (ISS) of a Northeast state of the United States.
Department of Children and Families. The ISS is a collaborative team of service providers from

11
various mental health agencies within the state, with the objective of facilitating trauma-
informed, gender responsive, and culturally sensitive treatment for children, adolescents, and
families.
A phenomenological, descriptive, qualitative approach was appropriate for this study
because it is conducive for the exploration of SBMHCs’ perceptions, along with their inner
subjective experiences about the phenomena of inquiry. Palinkas et al. (2013) suggested that a
research design should be a premeditated process throughout every research phase. Therefore,
the use of a descriptive, phenomenological, qualitative approach was useful to conduct semi
structured, face-to-face interviews. The approach assisted with the identification of a number of
SBMHCs working in a selected school in Connecticut, United States.
Interviewing SBMHCs provided answers to my research questions. Sutherland and
Cameron (2015) suggested that interviews provide the investigator greater access to insights and
clues and enhance a researcher's ability to interpret data as a replication of the subjective
experiences of participants. In addition, interviews allow the researcher to have questions
prepared in advance so that the investigator can improvise subsequent issues. Because of these
reasons, face-face interaction and rapport with SBMH services professionals provided an
opportunity for the flexibility to explore unexpected issues.
Operational Definition of Terms
The following are terms and definitions used in this study.
Disparities: Variations in quality of care and access provided to a minority patient
compare to the one received by a nonminority (Institute of Medicine, 2002).

12
Every Child Succeeds Act of 2015: A U.S. Act of Congress that improved upon the
reauthorization of the Elementary and Second Education Act. Every Child Succeeds Act of 2015
provides opportunity for children to succeed, through increased support for school districts,
teachers, and principals and by holding schools accountable for the progress of their students
(U.S. Department of Education, 2015).
School-based mental health (SBMH): Services that encompasses a range of assessment,
prevention, intervention, counseling, consultation, referral activities, and services provided to all
adolescents to ensure a safe and healthy learning environment (ASCA, 2015).
School counselor: Behavioral specialists who work in elementary, middle, and high
school settings to help all students achieve academically, develop healthy interpersonal/social
skills, and meet appropriate developmental milestones. School counselors collaborate with other
professionals within and outside the school to support all students to be productive (ASCA,
2015).
School nurses: Professionals specializing in advancing the wellbeing, academic success,
and lifelong achievement of students. School nurses promote positive student development,
providing care, health, and safety and actively collaborate with other professionals (American
Academy of Pediatrics, 2008).
Special education teachers: Educators with specialized skills in teaching students with
developmental, physical, and /or neurological delays. Special education programs in schools’
work with different disabilities and learning differences (National Association of Special
Education Teachers, 2015).

13
School psychologists: Individuals with specialized advanced degrees in mental health
learning and behavior. The primary job of school psychologists is to help children and
adolescents succeed academically, socially, behaviorally, and emotionally; they work in
partnership with families, teachers, school administrators, and other professionals to provide safe
and healthy learning environments (NASP, 2015).
Socioeconomic status (SES): SES refers to the measurement of educational attainment,
income level, occupation, privilege, power, and control. Societies commonly view SES from the
lens of an individual or group social class standing. Low SES include low academic
achievement, poverty, and unequal access to quality mental health care (Morgan et al., 2009).
Assumptions
Germannand and Aram (1996) argued that research assumptions are a methodological
tradition that enables the investigator to incorporate their sets of beliefs into the interpretative
framework to show the significance of the study. The assumptions of my research helped with
the process of recording and analyzing data, conclusions, and evidence. that SBMH counselor
participants work full time 32-4o hours in a school district in Connecticut and had the knowledge
and professional experiences of SBMH services. Another assumption was that study participants
provided honest opinions. I further assumed that the lack of extensive literature on adolescents'
SBMH service uses was attributable for the high prevalence of unmet mental health needs among
this target research population.
Scope and Delimitation
In this study, the goal was to examine SBMHCs’ perceptions of factors that may affect
adolescents’ use of services. Establishing scope and delimitation was necessary to ensure that the

14
study process of SBMH counselor's perceptions was focused and complete. Baybutt (2015)
asserted that scope and delimitation determine the extent of the research investigation and
compels inquiries to appropriate content. I collected data through face-to-face interviews with
SBMHCs who worked in a school district in Connecticut. SBMH services are not equal for a
variety of reasons. SBMHCs at different schools were not within the scope of this study.
SBMHCs who worked outside of the area may not describe the same lived experiences of
SBMHCs working with students from a school district in Connecticut. Additionally, this
qualitative investigation of the nature of this design may not be generalizable to other regions
and populations.
Limitations
Subjectivity is a concern for researchers. Ratner (1997) postulated that a researcher
subjectivity has potential negates objectivity in research because the researcher makes every
decision. Shelton, Smith, and Mort (2014) suggested that researchers must reflect on their values
and objectives to understand the influence it may have on their study findings. In this study, data
collection involved the use of semi structured, face-to-face interviews that had challenges,
including the possibility that my presence as a novice researcher could prevent the professionals
from responding openly and honestly. In addition, self-report of SBMHCs was limited. As a
result, the study findings were extrapolated exclusively from their perceptions. Therefore, I took
measures such as reflexivity to prevent bias. Shelton et al. pointed out that reflexivity helps the
researcher to reexamine previous assumptions and preconceived notions with new perspectives
on the phenomena of inquiry.

15
Significance
The study of SBMHCs’ perceptions about factors that may affect SBMH services was
critical to gain an understanding of the adolescent use of SBMH services. The prevalence of
unmet mental health needs of adolescents justifies the need for a more efficient SBMH services
that motivate adolescents from a school district in Connecticut to use services to improve their
overall mental and emotional wellbeing. Study findings may contribute to informing SBMH
stakeholders about teens’ SBMH services use. Insights from this study may provide information
for local school district principals, officials, and child and adolescents educators to develop
culturally sensitive, contextually relevant, and better outcomes for adolescents at-risks.
Social Change Implications
The study of SBMHCs’ perceptions has social change implications including bringing
greater awareness of the unmet mental health needs of adolescents to a school district in
Connecticut, educators, counselors, psychologists, teachers, nurses and others in the school
counseling setting. Such awareness may lead to the development of strategies to mediate
adolescent unmet mental health needs. Study findings may add to existing health services
literature on adolescents’ mental health. SBMH services hold promise for addressing
adolescents’ differing social needs and future aspirations, as well as confronting growing
disparities in service use.
Summary
SBMH services remain the de facto provider of mental health care to all adolescents. A
scant amount of literature was identified about SBMHCs’ perceptions of factors that may affect
adolescents’ services use. Due to an inadequate mental health care system and services, schools

16
in the United States face pervasive and intensive mental health needs (NASP, 2015). When
mental health services are inadequate, adolescents have worse short-term and long-term
outcomes or life trajectories. The problem disproportionately affects adolescents and minorities
of low SES (Gamble & Lambros, 2014; Ling et al., 2014; Substance Abuse and Mental Health
Services Administration [SAMHSA], 2015). Few adolescents are using SBMH. SBMH services
must improve to address the unmet mental health needs of the adolescents to change their lives
for the future. Incorporating SBMHCs’ experiences and perspectives as an integral part of the
agenda for reforming SBMH services may help educators and policymakers improve quality of
services.
Chapter 2 includes a literature review of research findings of the prevalence of mental
health issues and adolescents' use of SBMH services. The chapter starts with a historical
overview and characteristics of SBMH in the United States. Additionally, Chapter 2 contains the
description of research strategy, the pervasiveness of mental illness among adolescents, and the
theoretical framework that guided this study.

18
Chapter 2: Literature Review
Introduction
SBMH services are recognized as the first stop for parents and caregivers seeking help
for children and adolescents with emotional problems (Bear & Finer, 2014; Ramos et al., 2013).
Researchers, educators, school professionals, government, and community stakeholders have
been concerned about whether these services are adequate to address the 20-36% children and
adolescents with mental health needs (Bains & Daillo, 2016; Bear & Finer, 2014). SBMH
services are the cornerstone for addressing adolescent emotional wellbeing by helping
adolescents meet developmental milestones, develop coping skills, secure attachments, and
cultivate positive peer relationships (U.S. Department of Health and Human Services [HHS],
2015). Examining the perceptions of these professionals as change agents, while focusing on
factors affecting the use of services by adolescents, is a step toward addressing disparities in
service use by adolescents and creating improved outcomes
Historical Perspective
SBMH services in the United States have evolved over the years to meet the complex
mental health care needs of adolescents from diverse backgrounds. The first SBMH services in
the United States was established at the University of Pennsylvania in the late 1800s, during a
period of massive government and public reform that lasted through the 1930s (Collins, 2014).
This era saw an increase in school enrollment—annual academic year attendance increased from
135 days to 173 days (Collins, 2014). This period also saw industrialization and urbanization.
Reformers challenged school districts to address issues of health, industrial education, recreation,

19
and mental hygiene (Flaherty & Weist, 1999; Pumariega & Vance, 1999). Four factors prompted
the reforms: new child labor laws; immigration new scientific research; and the emergence of
psychology, social work, and education as recognized disciplines (Lourie & Hernandez, 2003).
Although these reforms paved the way for mental health services in schools, school-based
services were inadequate to provide services to every student. Mental health services were not
part of the educational system until decades later (Flaherty & Weist, 1999). These reforms
transformed the school staffing model from one dominated by teachers to one in which diverse
professionals came together to provide mental health services for adolescents.
Additional reforms introduced by the late 19th century was under the effect of educators
such as Richman, Dewey, and Adams. These individuals played a role in addressing the social
problems inherent to increasing student enrollment, including a lack of student motivation;
discipline problems; and cultural disconnects between teachers, adolescents, and other staff
(Flaherty & Weist, 1999). The reformers looked to create an educational system that was
responsive to adolescents’ needs and could address barriers to learning. During the same period,
school advocacy was further extolled by Kilpatrick, who advocated that classrooms promote
mental health awareness (Ramos et al., 2013).
The reforms proved successful enough to warrant funding for child guidance clinics in all
50 states by 1922 (Flaherty & Weist, 1999). These clinics were responsible for providing
interdisciplinary teams of professionals to care for children and their families. The clinics offered
affordable care to the needs of the individual child and family, while using different treatment
modalities that included psychodynamic psychotherapy, family therapy, crisis intervention, and

20
outpatient treatment (Ramos et al., 2013). Adolescents experiencing learning and behavioral
problems began to receive treatments in 1930 at various locations and resumed schooling when
stable (Flaherty et al., 1999). The changes in SBMH continued to have an impact on the mode of
mental health care delivery for adolescents.
Changes in SBMH services took place between the 1960s and the 1990s, because of
social norm transformations that occurred during that period (Flaherty et al., 1999). These
changes included the emergence of child/adolescent medical psychiatry and the passage of the
Individuals with Disabilities Education Act (IDEA) of 1975. The IDEA legislation emphasized
school district accountability for the social and emotional wellbeing of students (Pumariega &
Vance, 1999). Prior to these changes, mental illness among children and adolescents did not
elicit researchers’ interest or public discussions. The expansion of mental health clinics in
schools continued into the early 2000s, increasing public awareness of the prevalence of mental
illness and its consequences among adolescents. Ramos et al. (2013) noted that during the early
2000s, there was an increase in suicide, homicide, substance abuse, child abuse, teenage
pregnancy, school dropout rates, and adolescents’ crime (Ramos et al., 2013).
The heightened awareness led to studies on a need for policy and practice changes
(Pumariega & Vance, 1999). Lourie and Hernandez (2003) called for a policy shift, noting that a
lack of mental health policy for children in the United States made it difficult to identify children
with behavioral needs in order to provide the necessary technology to ensure that children and
adolescents receive adequate and quality mental health services. The increase in research

21
findings and recommendations for further reform in the mental health delivery system spurred
presidential action.
President George W. Bush appointed the New Freedom Commission (NFC) in 2003 to
assess the United States . mental healthcare delivery system and make policy recommendations
for improvement (Mills et al., 2006). The NFC deduced that the system was “fragmented,” “in
disarray” and in need of reform (Mills et al., 2006, p. 150). The commission recommended goals
for improving mental health care that included a national campaign to reduce the stigma attached
to mental health care, suicide prevention programs, advancement of school mental health
programs, and screening interventions for mental health and substance use disorders (New
Freedom Commission, 2003). The impact of these recommendations resulted in the growth of
SBMH programs to address adolescents’ mental health needs.
Characteristics of School-Based Mental Health Services
SBMH services are entry points for addressing adolescents’ mental health needs. The
features of SBMH in the United States vary by region, locale, and school size (SAMHSA, 2015).
Although there are 83,000 SBMH programs in the United States. public elementary, middle, and
high schools, disparities exist based on school size and locale (SAMHSA, 2015). SBMHCs
provide direct and indirect intervention services to support the life skills and healthy emotional
development of a diverse student population (ASCA, 2015). In the United States, 20-25 % of
adolescents in U.S. school districts experience higher levels of unmet mental health needs, of
which only 36% receive services (Bains & Diallo, 2016). A significant number of children and
adolescents with mental health problems are exposed to continuing poverty, residential

22
instability, limited access to services, and poor quality of mental health care for a variety of
reasons (Bains & Diallo, 2016; Gamble & Lambros, 2014). These reasons may be linked to the
academic achievement gap, which remains a concern for all school districts in the United States.
According to the U.S. Census Bureau (2014), 43% of adolescents live in households where
English is not the primary language, 37.6% live below the poverty line, and 92% receive free or
reduced lunch. Because of these limitations, SBMHCs face challenges in meeting the
psychosocial needs of adolescents. SBMH services a part of addressing adolescent mental health
needs, through the provision of various services.
SBMH Services Categories
1. Assessment for emotional or behavioural problems or disorders, including
behavioural observation, psychosocial assessment, and psychological testing
2. Behaviour management consultation (teachers, student, and family)
3. Case management (monitoring and coordination of services)
4. Referral to specialized programs or services for emotional or behavioural problems or
disorders
5. Crisis intervention
6. Individual counselling/therapy
7. Group counselling/therapy (SAMHSA, 2015)
Eligibility for SBMH Services
SBMH services are open to all students; however, eligibility for services vary across
schools due to differences in school characteristics. SBMH services serve the poor, urban,

23
immigrants, uninsured, and underinsured adolescents within the context of family, culture, and
environment (Connecticut Department of Health, 2015; Gamble & Lambros, 2014). Although
services are available to all students irrespective of insurance status or ability to pay, in order to
be eligible, SBMH must be located in the district students attend school.
Another characteristic of SBMH services is that funding streams appear fragmented and
not well defined (SAMHSA, 2015). A proportion of SBMH funding comes from the Special
Education Act, known as IDEA, State Children Health Insurance Programs (SCHIP), and
organizations with various missions. SBMH in low SE districts face obstacles to delivery and
coordination of services because of restrictions imposed by funding sources on the types of
services and duration (Gamble & Lambros, 2014; SAMHSA, 2015). Overall, SBMH support
schools to improve the mental health wellbeing of adolescents.
Research Strategy
The literature review involved an active collaboration with Walden University librarians
to identify articles in which researchers explored factors that may affect SBMH service use and
that included the perspectives of SBMHCs. Multiple databases that included Education Research
Complete, PsycINFO, Nursing, School Health, Proquest Central, Medline, SocINDEX with full
text, Thoreau multi-Database, and Google Scholar were used to locate peer-reviewed articles and
original research on SBMH services. Articles written for, and disseminated by, professional
organizations such as the American Academy of Pediatrics, ASCA, National Association of
Nurses, and the NASP were included as resources for this study.

24
The search process began with key terms such as mental health services, school-based
mental health professional perceptions, and characteristics of SBMH services. Synonyms were
used to capture the concepts from the research questions on factors that affect the use of SBMH
services by adolescents according to SBMHCs. Some articles used in this study are within 5
years. Some older articles were included later. The review yielded several significant articles
that, according to SMBH professionals, identified factors affecting use of school-based mental
health services.
Theoretical Framework
In accessing medical and psychological services, the patient of the client has to decide to
attend such services or seek help. Help-seeking behavior is acknowledged in the medical and
psychological service field as a term to describe the behavior of a patient reporting for care. Help
seeking is influenced by different factors such as cultural factors, attitudes and beliefs regarding
illness, and the realization of the patient that help is needed (Barry, Doherty, Hope, Sixsmith, &
Kelleher, 2000). The general theory of help seeking, as developed by Mechanic (1978), was used
in other studies.
Other theories or models of help seeking include rational choice theory, which focuses on
the people who seek help. This model has its roots in the biomedical model that became popular
in the late 1700s. Symptoms were viewed as physiological facts (Armstrong, 1999). In this
model, the medical personnel drove the process as they were perceived as being knowledgeable
and as someone who knew the best way of managing the illness. (Armstrong, D., Bird, J, Fry, J.,
& Armstrong.,1992) This perspective sees help-seeking behavior as a rational choice of people

25
after weighing the benefits and their decision to seek help (Pescosolido & Boyer, 1999).
Researchers have explored reasons why people delay seeking treatment. Several theories
regarding help-seeking behavior were published including Andersen’s social behavior model,
Azeen’s theory of planned behavior, and the health belief model of Rosenstock (Armstrong,
1999). Another model of health-seeking behavior is the dynamic model that asks when and in
which manner (how) people seek help. The dynamic model has its roots in the insights of
sociologists and anthropologists (Pescosolido & Boyer, 1999). This view took into consideration
that the individual interprets the facts about illnesses to him or herself and that this understanding
leads to the recognition of being ill. The general theory of health-seeking behavior of Mechanic
(1978) was used to guide this study.
Mechanic’s (1978) general theory of help seeking provided an entry point into the
discussion. Mechanic outlined 10 key reasons that individuals seek help to resolve health issues.
The 10 key reasons are as follows:
1. When the person is certain there are noticeable signs of abnormality and symptoms
2. The degree to which the person views the seriousness of the symptoms of his or her
illness
3. How well the person copes with the signs of his or her health issues
4. How often the symptoms reemerge and are prolonged
5. How long the person can endure the symptoms
6. The degree to which the person understands his or her condition and culturally held
beliefs about the health issue

26
7. The person denies the existence of the health issue because of basic needs
8. The person weighs whether dealing with the health issue now or later will affect his
or her immediate needs
9. When the person develops a different explanation for his or her symptoms
10. Proximity to care, financial cost, psychological cost, and treatment resources
The theoretical model of help seeking is vital to improving services for SBMH services
for all adolescents. The model includes the reasons that may affect adolescents’ use of SBMH
services. Researchers have documented the prevalence of psychiatric disorders among
adolescents, although a significant percentage of these adolescents had no contact with mental
health professionals (Gamble & Lambros, 2014). A lack of vision or direction in the SBMH
system is a contributor to unmet care needs (Mills et al., 2006). SBMHCs’ perspectives were
essential to achieve a more collaborative approach to addressing current mental health care
delivery to adolescents.
Mechanic’s (1978) theory offers an effective approach for SBMHCs. SBMH
professionals worked in alignment with the 2003 President’s New Freedom Commission goal to
advance SBMH services (Mills et al., 2006). Lindsey et al. (2013) applied the help-seeking
model to study African American adolescent service needs and barriers to treatment. Lindsey et
al. concluded that interventions targeting “expectancies and social norms” might increase urban
adolescents and their families’ connections to mental health services (p. 1). Additionally, social
connectedness that consists of social integration and support was found to reduce suicide risk,
because of protective factors that enhanced psychological wellbeing, positive behavior

27
reinforcement by others, and social acceptance (Wyman et al., 2010). SBMH professionals could
help promote an environment where adolescents with identifiable mental health disorders feel
comfortable enough to seek services.
Role of School Special Education Teachers
Special education teachers play a role in the learning and development of adolescences.
When a student presents with mental health problems in the classroom, the teacher must be able
to deal with the distraction and stress that are likely to occur for both the teacher and other
students (Milvancevic & Jovicic, 2013; NASP, 2014). The role of special education teachers in
student learning and emotional wellbeing creates an appreciation for the combination of
intellectual, social, and emotional education, all linked to safer schools, healthy character
building, positive wellbeing, and academic success (Paternite & Johnston, 2005). Ecological
factors in the school, coupled with teacher support, stress levels, and organizational factors,
interact to affect academic and psychological outcomes for adolescents (Lynn, McKay, &
Atkins, 2003). The effect of special education teachers is an important protective factor in
mediating these ecological factors in school environments (Lynn et al., 2003). Special education
teachers help schools identify problem areas and intervene to reduce harmful behaviors.
Additional functions of special education teachers include monitoring and making referrals to
other SBMH professionals including school psychologists.
Role of School Psychologist
School psychologists play a role in the delivery of school mental health care services to
adolescents. Although their job description has evolved over the years as mental illness among

28
adolescents is increasingly identified, school psychologists primarily help adolescents to develop
academic, social, and life skills while providing prevention, early intervention, and general
mental health services (NASP, 2015). School psychologists play a role in coordinating school
discipline programs, such as suspensions, as well as help to improve school attendance and
reduce disruptive classroom behavior. Through their collaboration with other school
professionals and families, school psychologists participate as members of an interdisciplinary
team in developing, evaluating, and implementing a comprehensive mental health screening
system that addresses a range of student mental health issues (Splett, Fowler, Weist, McDaniel,
& Dvorsky, 2013).

29
Researchers have argued that expanding the role of school psychologist can improve SBMH
services (Eklund, Vaillancourt, & Pedley, 2013; Graves, Proctor, & Aston, 2014; Splett et al.,
2013). The need to improve services for all adolescents may require the active participation of
school psychologists in discerning SBMH programs. School psychologists with direct
professional interactions with adolescents are in a position to affect student behavior.
Other researchers suggested that universal screenings should innovate to change current
system of mental-health intervention that rely on student risk levels (Splett et al., 2013). School
psychologists’ skills position them beyond the traditional role of assessment, to a role that
contribute to best practice strategies aimed at preventing mental health concerns among
adolescents (Splett et al., 2013). Urban school psychologists’ perspectives differ from school
psychologist who work in non-urban school settings (Graves, Proctor, & Aston, 2014).
Moreover, the emerging role of school psychologists involves addressing adolescents’ unmet
needs in the community (Graves et al., 2014). These studies underscored and confirmed the need
to explore perceptions of SBMHCs about factors affecting adolescents, using or not using
services. School psychologists may help shape SBMH services to meet student needs and
improve outcomes. As a result, their expertise and perspectives warrant consideration. School
psychologists work in collaboration with other professionals such as school counselors to
improve the wellbeing of adolescents.
Role of School Counselors
School counselors hold a master’s degree or Ph.D. in school counseling or have the
substantive equivalent in combined education and experience (ASCA, 2015). School counselors

30
assume various roles in providing comprehensive services to adolescents. The ASCA model
specifies roles for school counselors and suggests that equitable access to rigorous education
following evidence-based practice for all adolescents is essential (ASCA, 2015). A crucial
element in the role of a school counselor is ensuring positive academic outcomes for all
adolescents by counseling and collaborating with special education teachers. School counselors
can help social workers focus SBMH services by working with at-risk adolescents via individual
and group counseling, as well as working with educators to improve adolescents’ academic
performance (Lynn et al., 2003). Understanding perceptions of SBMH service professionals such
as school counselors may provide useful information that may help improve the outcomes and
life trajectories of adolescents. School administrators can maximize the role of school counselors
through planning and designing SBMH programs that address adolescents’ current mental health
care needs. School counselors work in concert with school nurses to identify adolescents with
mental health needs.
Role of School Nurses
Historically, school nurses have played essential role in SBMH services. School nurses
are involved in several activities within school-based health centers in the United States
(National Association of School Nurses [NASN], 2015). Their primary function of nurses
includes supervision, health education, clinical decision making, health screenings; and
coordination of care for adolescents who require advanced medical attention (NASN, 2015). The
role of nurses in the mental health care of adolescents is invaluable. In some underserved school
districts in the United States, Advance Practicing Registered Nurses, (APRNs) who specialize in

31
psychiatry provide mental health interventions, reduce risk, build partnerships, increase access to
services; improve the quality of services, and work to reduce stigmas surrounding mental
healthcare services (Grossman, Laken, Stevens, & Hughes-Joyner, 2007) One survey of a New
Mexico public school nurse workforce described their school nurses’ involvement in managing
adolescents’ mental health crisis (Ramos et al., 2013). These researchers found that during prior
school years, two thirds of school nurses had responded to adolescents’ mental health
emergencies, and were involved with cases of child abuse, neglect, depression, and violence at
school. The school nurse function extends beyond addressing adolescents’ physical health care
needs and includes attending to the psychological and emotional needs of adolescents (Bains, &
Daillo,2016). The understanding of the perspectives and roles of school base nurses was
important to identify themes and
Common Mental Health Problems Among Adolescents
Families, educators, communities, and the government are aware that mental health is a
serious public health concern. A substantial number of adolescents cope daily with the emotional
problems that affect their learning abilities and peer relationships (Milovancevic & Jovicic,
2013). These emotional problems may result from family dysfunction and other psychosocial
stressors that schools must address while providing a safe learning environment. There is
evidence that emotionally unstable children fail to achieve their full potential (NASP, 2015). In
United States schools, common mental health problems associated with poor learning outcomes
include depression, anxiety disorders, attention-deficit/hyperactivity disorder, and substance use
disorders (NASP, 2015). These externalizing and internalizing conditions are described below.

32
Depression
Childhood depression is an internalizing condition that affects a significant number of
U.S. adolescents. Depression features include unhappiness, sadness, and stress, thus resulting in
marked impairment of the individual’s activities of daily living and results in possible thoughts
of suicide (Ruderman, Stifel, O’Malley, & Jimerson, 2013). The CDC (2015) and Cuellar
(2015), found that the prevalence of depression among adolescents demonstrated that depression
occurs in 4.6% of children and 8.3% of adolescents, with 14% to 20% chance that children and
adolescents will receive future diagnoses of other depressive symptoms (CDC, 2015; Cuellar,
2015). In 2010, 2.1% of children and adolescents received diagnoses of depression (CDC, 2015).
Diagnosing and treating adolescents who present with depressive symptoms in schools is critical
in reducing the risk factors for suicide, a leading cause of death among adolescents (CDC, 2015).
The results of a national survey of high school students revealed that 16% of adolescents
considered suicide as an option for resolving feelings of sadness and hopelessness. Another 13%
reported having an actual plan to commit suicide, while 8% wanted to take their own life within
12 months of the survey (CDC, 2015). These survey results indicate that there are unmet mental
health needs of adolescents.
Childhood depression is a debilitating public health concern that negatively affects
children and adolescents daily. Treatment of childhood depression often falls on the shoulders of
SBMH service professionals. As a result, SBMHCs’ role is key to systematic change. In
addition, the role helps school administrators, policymakers and other stakeholders understand
depressions’ multidimensional etiology and what promotes adolescents’ emotional-wellbeing as

33
they interact with school, home and other social and cultural environments (Batterman, 2015;
Cuellar, 2015). SBMH counselor’s perceptions may contribute to the creation of different
approaches that manage and support adolescents who are at-risk for developing depression.
Adolescent depression is caused by an interplay of sociocultural, biogenetic, personality,
family, emotional, cognitive and behavioral patterns (Ruderman et al., 2013). Social-emotional
difficulties have been associated with poor academic achievement. In a study comparing 130
Mexican school children with learning disability (LD) severity and risk factors to 130
adolescents without LD, researchers found that 22% more adolescents with LD experienced
anxiety and 11.5% more experienced depression than those without LD (Gallegos, Langley, &
Villegas, 2012). Adolescents presenting with depression could benefit from increased
involvement of SBMH service professionals in administrative decision making about delivering
mental health care to adolescents.
Anxiety Disorder
Anxiety is another internalizing chronic disorder that can present in different forms and
may be comorbid with panic disorder, agoraphobia, specific phobia; social anxiety disorder,
selective mutism, generalized anxiety disorder, medically-induced anxiety, substance-induced
anxiety, and other unspecified anxiety disorders (Cuellar, 2015; Gallegos et al., 2012; Gobriel &
Raghavan, 2012; McCallum-Clark, 2013). Addressing the prevalence of anxiety disorder among
adolescents is important to administrators, special education teachers and families, because
anxiety disorder is a significant contributor to academic failures and to social and emotional
development.

34
The causes of childhood anxiety have been attributed to affective variables such as self-
image, the child self-concept of their environment, motivation, temperament; loneliness, and
depression (Gallegos et al., 2012). According to the 2015 CDC National Mental Health
Surveillance Report (CDC, 2015), 3% of U.S. school-age children have been diagnosed with
anxiety. The prevailing high incidence of anxiety disorder among adolescents has an attendant
inverse relationship to both physical health and academic achievement. SBMH service
professionals play an important role in implementing interventions to reduce the negative effects
of anxiety conditions on adolescents.
Anxiety disorder is the most prevalent psychopathology in children (Martinez & Erickan,
2008; Paulus, Backes, Sander, Weber, & Gontard, 2014). Most troubling is that anxiety
disproportionately affects adolescents with co-morbid intellectual disabilities and autism
compared to intellectually disabled children and young people without autism (Martinez &
Erickan, 2008; Paulus et al., 2014). In a study of the prevalence of anxiety disorders among 150
metropolitan children and young people in the United Kingdom, Gobrial and Raghavan (2012)
found significant differences between intellectually disabled children and adolescents with
autism, and those without autism. This finding has implications for assessing anxiety disorder
among children and adolescents through collaboration between SBMH services professionals
and others within the system, using a team approach toward improving children and adolescents’
physical and academic health.
Adolescent mental health problems are increasing and addressing the prevalence of
mental health disorders among adolescents is important. Delaney and Smith (2012) asserted that

35
adolescent mental health concerns have future adverse consequences that affect adolescents’
socialeconomic status as adults, including educational levels, the number of productive weeks
worked per year, and individual and family income (Delaney & Smith, 2012). The researchers
suggested that designing and implementing effective interventions could help reduce the long-
term psychological and economic costs of anxiety, on adolescents and their families.
Attention Deficit Hyperactivity Disorder and Attention Deficit Disorder
Attention-deficit disorder (ADD) and attention-deficit hyperactivity disorder (ADHD) are
among the most common mental health disorders affecting school-aged children worldwide
(Grilo, Henriques, Correia, & Grilod, 2014). ADHD consist of three subtypes: hyperactive-
impulsive, inattentive and combined hyperactive-impulsive and inattentive (National Institute of
Mental Health [CDC], 2013). ADHD affects 1% to 20% of school-aged children and
adolescents, along with a substantial number of undiagnosed cases or under identified
schoolchildren with sub-threshold ADHD symptoms (Fabiano et al., 2013; Grilo et al., 2014).
Researchers found the prevalence rate of ADHD to be higher among boys at 66.7%, compared to
that of girls at 33.3% (Ventkata & Panicker, 2015). Similarly, a study designed to establish the
association of ADHD with childhood allergic diseases, found that children with ADHD are more
susceptible to asthma and allergic rhinitis (Kim, Ha, Oh, Kim, & Paik, 2014). Another study
found a significant connection between ADHD and obesity among school-aged children (Kim et
al., 2014). These study findings indicated that ADHD negatively affects adolescents’ daily
functioning in school and at home.

36
The etiology of ADHD shows that it is a neuropsychiatric disorder caused by genetic,
biochemical, and environmental factors (Fabiano et al., 2013; Grilo et al., 2014; NIMH, 2013).
ADHD can be mistaken for other health problems because symptoms of inattention, hyperactive
and impulsive subtypes manifest differently. For example, children and adolescents who present
with hyperactivity and impulsivity exhibit emotional and “out of control” behaviors at greater
degrees.
The treatment of ADHD in children and adolescents has historically focused on reducing
symptoms and improving their ability to function (NIMH, 2013). Treatment includes the use of
different models of psychotherapy, psycho-education, and combinations of medication and
therapy (NIMH, 2016). Medications, such as stimulants, have calming effects on adolescents
with ADHD, which allows them to focus, work and learn. Yet, these medications have high
incidences of misuse by adolescents who self-medicate for focus and faster learning.
Lian-Yu et al., (2016) studied the trends of prescription drugs misuse involving Adderall
and Ritalin (common ADHD medications), by examining three sets of data: National Diseases
and Therapeutic Index, National Survey on Drug Use and Health, and Drug Abuse Warning
Network, to identify treatment visits that involved the prescription of Adderall for adults and
adolescents. Between 2006 and 2011, non-prescribed use of Adderall increased by 67% and
emergency room visits by 156 %, while treatment visits for adolescents declined (Lian-Yu Chen
et al., 2016). Adderall and other types of ADHD medications have risks associated with their
use, including possible side effects such as decreased appetite, sleep problems, repetitive

37
movements, hearing voices; cardiovascular problems, hallucinations, and mania (NIMH, 2013).
Misuse of prescription drugs by adolescents is a significant concern.
Substance Use Disorder
Substance use disorder is a problem among school-aged children. The high incidence of
substance use in this population has social, financial, and health consequences, including but not
limited to, poor academic performance, mental disorders, accidents and injuries, overdose;
addiction, and unintended pregnancy (CDC, 2015). Research indicates that early exposure to
substance use significantly correlated with substance use disorder in adulthood (Finn, 2006;
Sznitman, Dunlop, Nalkur, Khurana, & Romer, 2011). Teen substance use is widely attributed to
the contextual developmental stage of adolescence and an underlying indicator of undiagnosed
mental health problems.
The Center for Disease Control and Prevention National Surveillance Report (2015) on
alcohol, drug use, and academic achievement results, indicated that 8.3% of adolescents reported
substance use disorder during the past year. The interview questions focused on identifying
emotional problems associated with adolescents’ substance use, previous attempts to decrease
use, tolerance, withdrawal, and drug use related activities. Substance abuse disorder declined
from 8.9% in 2002 to 6.9% in 2011 (CDC, 2015), but remains a concern for families,
administrators and policymakers.
In a study of positive school climates and student drug testing, Sznitman et al. (2011)
found that positive climate decreased personal substance use in adolescents. The researchers
suggested that positive climates in schools help adolescents feel respected. Adolescents are

38
likely to follow adult recommendations if they feel they have rapport with the adult (Sznitman et
al., 2011). Modeling and providing safe environments where adolescents can excel academically
is an important role of SBMH professionals.
Researchers Finn and Willert (2006) surveyed 103 teachers from middle and high schools
about their perspectives on adolescent alcohol and drugs use. The researchers found that student
substance use occurs during the school day and outside school hours. They state that the “drug-
free school zone” is far from a reality. The researchers also found that teachers questioned the
effectiveness of school drug policies, and 43% of teachers were uneasy about responding to
perceived student drug use in school. SBMH service professionals need to be involved in the
discussions of school and classroom drug use because schools are not immune to illicit drug
activities.
Substance abuse statistics vary across ethnic groups. Aarons, McCabe, Gearity, and
Hough (2003) examined ethnic variation in drug use for 936 adolescents aged 13 to 18 years.
Aarons et al. (2003) studied a random sample of adolescents who were actively receiving
treatment in one of five care sectors. The researchers found significant differences in use rates by
the adolescents. African-American adolescents were less likely than White adolescents to meet
the criteria for lifetime substance use. They also found that White and Latino adolescents have
the highest rates of substance use compared to other ethnic adolescents. The researchers suggest
that recognizing how drug use varies across ethnic groups is essential to providing equitable
opportunities for treatment.

39
Over the years, educators, families and school administrators have recognized that
substance abuse by adolescents pose substantial public health concerns. Substance abuse
program were set up to target at-risk adolescents. Whether these programs are effective in
reducing students drug use remains the subject of research. A pre-post intervention comparison
group design study of Missouri adolescents was conducted from two school districts composed
of eighth to tenth grade adolescents (Williams, Barnes, Holman, & Hunt, 2014). The intervention
group consisted of 14.7-year old adolescents who were considered at-risk due to past behavioral
problems, poor academic performance, and unstable home life. The control group consisted of
15.6-year-old in grades eight through ten from a third district. Williams et al. (2014) found that
rural adolescents have significant substance abuse problems that warrant the attention of the
scientific community and professionals. They also found that a short-term, group-matched
mentoring program had significant positive influence on reducing substance use for at-risk
youths (Williams et al., 2014). The researchers noted that social norms do not change instantly
and that successful prevention efforts have long-term positive impact for at-risk youth and
decrease demand for scarce resources.
Similarly, Sharma and Branscum (2013), studied 18 school-based substance abuse
prevention programs that included 12 different interventions. Fifteen of the 18 studies used
randomized controlled trial designs. Seven of the studies showed statistically significant changes
in substance use across pre- and post-intervention. The change was to use program theory to
develop program objectives, choose program activities, set timing of intervention and replicate

40
intervention components that work. The researchers recommended theory-based early prevention
interventions in schools, and measured the constructs using psychometric tools.
Researchers Lizuka, Barrett, Gillies, Cook, and Marinovic (2014) conducted a study of
72 teachers and 25 non-teaching staff from low SE schools to test the impact of teaching social-
emotional skills on adolescents. The researchers concluded that after training in the new skills,
student anxiety levels declined. Mallett (2014) found that mental health disorders are associated
with profound school and education difficulties for children and adolescents. Substance use
disorder is a major public health concern that is associated with poor academic performance,
social, financial and negative health consequences (Sharma & Branscum, 2013). Early detection
and intervention with adolescents who present with substance disorder may help school
administrators, educators and policymakers decrease the prevalence of substance use among
adolescents. SBMH counselor’s involvement and insights may play an important role in this
effort.
Previous Research
In the early 2000s, there was an increase on studies focusing on school based mental
health services to improve mental health care for all students in the United States schools
(SBMHS). Subsequently, there was a decline in research that focus on access and quality of
services provided to adolescents, (Ling et al., 2014). The decline in literature created a gap and
awareness of the need to examined School-Based Mental Health Counselors perceptions about
factors and barriers that affected adolescents’ use of service. There has been minimal impact
toward improving the use of SBMH services because of these research-driven initiatives.

41
Consequently, school-based mental health literature has failed to report accurate, generalizable
data specific to urban school adolescents’ populations (Gamble & Lambros, 2014). However,
recent research trends are helping to identify unmet needs of groups and ways to improve
services.
Gamble and Lambros (2014) examined the perspectives of 39 SBMH providers who
serve urban, suburban, and diverse groups to help families gain access to quality mental health
care. The researchers found that effort to promote minority access was stymie by culturally
related factors. Nonetheless, the researcher opined that databased tracking, decision-making, and
staff development are crucial ingredients to improve service delivery. Ling, Okazaki, Tu, and
Kim (2014) examined the unmet mental health care needs of Asian Americans adolescents from
urban communities, in an afterschool and mental health setting. The purpose of the research was
to gain the perspective of service providers on the challenges that providers faced in meeting the
psychosocial needs of Asian adolescents. The researchers concluded that challenges facing
providers included complicated family dynamics, structural stressors, social stigma and
discrimination.
A study by Wegmann, Powers, and Blackman (2013) consisted of focus groups of
caregiver and teacher perspectives in a pilot SBMH project in an urban school district with low
standardized scores and high level of student need. The purpose of the research was to find ways
to support vulnerable families through SBMH. The researchers purposely selected all the
caregivers and teachers to participate. The implication of this study according to the researchers,
is that collaboration between SBMH professionals, teachers, and families is imperative to meet

42
adolescents’ mental health needs. Despite the noble attempts of these researchers to identify
group specific disparities, the perspectives of SBMHCs appear unknown regarding factors that
affect adolescents use of services.
A systematic literature and synthetic review of 47 evidence-based studies (Bains& Diallo,
2016; Rones & Hoagwood, 2000) was conducted between1985-1999 and 2016 on services
delivered in U.S. schools. The researchers of this review were propelled by the significant role of
schools in addressing adolescents’ emotional and behavioral problems, a desire to document a
fragmented and inconsistent literature, and the increasing number of children with unmet needs.
They concluded that, while there is substantial evidence to support the impact of SBMH
programs on reducing emotional and behavioral problems, 20-25 % are affected by mental health
issues, only 36 % receives mental health services, and differences exist among adolescents
(Bains & Daillo, 2016; Rones & Hoagwood, 2000). Understanding the SBMHCs’ perceptions
may help to uncover the differences.
Concepts embedded in the Re-ED model of emotionally disturbed children was examined
from an ecological perspective by Paternite and Johnston (2005) focusing on how contextual
variables interact in the student’s environment. Recognizing the often-uneasy alliances between
educators and mental health professionals, these researchers suggested that improvements are
possible through dialogue and collaboration. By changing professional perceptions, a more
cohesive interdisciplinary approach could emerge to create better public awareness and new
school-based programs that address the burden of adolescents’ mental health disorders.

43
Furthermore, the researchers suggested redefining the term educator to reflect a broad spectrum
of different initiatives and close the gap in adolescents’ use of SBMH.
Two focus groups taken from a random sample of 296 English secondary schools
participated in a study to measure emotional health levels among adolescents ages 12 to 14.
Results showed that schools provided some emotional support (Kidger et al., 2009). The type
and quality of support varied significantly (Kidger et al., 2009). Adolescents indicated their
preference for a more confidential approach from helping sources and empathy from staff. They
also identified a need to assess school environments when looking for causes of distress. Kidger
et al. (2009) found the school environment as a strong factor affecting student use of SBMH
services.
Substantiating the impact of environmental factors, Wuet et al. (2010) performed a
bivariate and multiple logistic regression analysis with data from the 2000 National Household
Survey on Drug Abuse composed of 877 adolescents aged 12 to 17 years of age with a history of
suicide attempts in the past 12 months. The survey results showed that fewer than 45% of the
adolescents reported using mental health services during the past 12 months. Racial/ethnic
minorities used fewer inpatient and outpatient services than Whites did, even when variables
such as individual, family and other characteristics are considered. In addition, having a poor
self-concept of health, and living in a single-parent home in a low SE environment were
associated with use of inpatient services (Wu et al., 2010). Female gender, family income,
participation in extracurricular activities, and the presence of anxiety or disruptive disorders were
associated with greater use of outpatient services. The researchers concluded that even though

44
SBMH services have the capacity to reach adolescents with suicidal tendencies, there are still
barriers to providing quality services.
Thirty-nine school psychologists from two school districts participated in 11 focus groups
that explored their professional practices and the factors that they believed affected access or
created barriers to SBMH services (Suldo, Friedrich, & Michalowski, 2010). Their analysis
showed that factors such as school environment, insufficient training, and lack of support from
district administrators and school personnel impede delivery of services. The researchers
suggested that school psychologists take proactive steps to increase their role in SBMH services.
When it comes to allocating financial resources, district administrators and school personnel
should collaborate with psychologists.
Other studies have examined the role of racial/ethnic disparities as an important factor in
SBMH services use. Caporino, Chen, and Karver (2014) measured acculturation, perceived
causes of depression, and treatment acceptability to compare differences in 67 female high
school adolescents’ attitudes towards depression treatment. Of the total participants, 54% were
Hispanic and the remaining were non-Hispanic Whites. The researchers concluded that there
were more similarities than differences between ethnic groups in favoring treatment. In contrast,
Bains (2014) examined disparities in mental health services utilization by conducting qualitative
studies of African-American adolescents’ goals when seeking help from SBMH services. The
researcher concluded that, unlike adults, adolescents consider the opinions of those close to them
before seeking help. Expanding on this insight, Betancourt, Frounfelker, Mishra, Hussein, and
Falzarano (2015) provided additional qualitative perspective in their study of perceptions of

45
mental illness and help-seeking behaviors among Somali Bantu and Bhutanese refugees. The
researchers found that the Somali Bantu and Bhutanese refugee adolescents faced unique
challenges in using services and would require culturally sensitive programs to address their
unmet care needs. Bogartet et al. (2013) examined the impact of perceived racial/ethnic
discrimination on health outcomes. They found that perceived racial prejudice was associated
with problem behaviors among African-American and Hispanic preadolescents and adolescents.
Summary
SBMH services are the cornerstone of mental healthcare delivery for adolescents in the
United States. SBMHCs provide a broad spectrum of assessment, prevention, intervention,
counseling, consultation, and referral services (NASP, 2015). Understanding the factors that
affect adolescents use of these services was important to create and provide evidence-based
programs to improve service delivery and eliminate access barriers for adolescents in need.
My research questions explored SBMHCs' perceptions of the services that they provide
to adolescents. Insight developed from this study may help educators, school districts, and
policymakers identify barriers to the use of SBMH services, learning and development. This
literature review yielded diverse research findings about past efforts to close a gap between
adolescents’ need for and use of SBMH services. Previous studies have examined perceptions of
different stakeholders regarding the services provided. The perceptions of SBMHCs about the
differential needs of adolescents provided rational for this study.
Chapter 2 included descriptions of specific steps I used to search the Walden University
Library resources to access and identify peer-reviewed literatures relevant to this study.

46
Although the literature search revealed minimal research on the phenomena of inquiry, it
confirmed that a gap existed in SBMHCs perceptions about adolescents’ use of services. Chapter
3 followed with the description of the research design and rationale, the participants, research
questions, data collection techniques; data analysis and ethical considerations.

47
Chapter 3: Research Method
Introduction
The overarching objective of my study was to understand the in-depth experiences and
perceptions of SBMHCs about adolescents’ use of services in a school district in Connecticut,
United States. Additionally, the purpose of the study was to discover SBMH perspectives of
factors that may affect adolescents' use of services. SBMHCs’ views, as change agents, may
advance policies that improve outcomes and adolescents’ life trajectories. Chapter 3 includes the
rationale for using the qualitative methodology to explore research questions for this study. In
this chapter, I describe the role of the researcher and bias prevention strategies. The chapter
concludes with a discussion of previous studies that employed descriptive phenomenological
research, the study participants, data collection methods used, data analysis, and ethical
considerations
Research Design and Rationale
A study of SBMHCs’ perceptions was the first step to examining how, why, and what
motivates adolescents to use services. I used descriptive, qualitative, phenomenological methods
to obtain in-depth information from these counselors. Phenomenological qualitative design
provided the best available lens for investigating the daily experiences of SBMHCs working with
adolescents. Researchers use phenomenological designs to ascertain the quality of the collected
data and analyze its meaning (Kroese, Rose, Heer, & O’Brien, 2012). Qualitative research
designs offer researchers flexibility in recruiting participants because it allows the use of

48
purposive sampling (Gentles, Charles, Ploeg, & McKibben, 2015). Researchers can use their
expertise to select individuals who can provide enough information for data analysis.
Previous scholars have used descriptive, phenomenological research to explore the
perceptions of mental health service professionals. Kroese et al. (2013) used a phenomenological
approach to gain an understanding of the experiences of mental health service users and the
professionals working with them. Similarly, Bornsheuer, Henriksen, and Irby (2012) used
phenomenology to investigate the perceptions of mental health care of purposefully selected
Christian church members. To gain an in-depth understanding of mental health services provided
to members, Bornsheuer et al. conducted face-to-face interviews with 14 participants to identify
commonalities and differences within their stories, including the importance of relationships,
knowledge of providers, and use of religious practices in counseling.
Gamble and Lambros (2014) used phenomenology to examine the lived experiences of
school-based mental health providers who served students in urban, suburban, and ethnically
diverse settings. Rutherford, McIntyre, Daley, and Ross (2012) conducted eight semistructured
interviews, using descriptive phenomenology to explore mental health service providers with
experiences providing care to Lesbians, Gays, Bisexual and Transgenders (LGBT) patients.
Study participants were from diverse backgrounds including psychiatry, social work,
psychotherapy, and psychology.
Flynn, Duncan, and Evenson (2013) used interviews and journal analysis to study the
career development process of nine 18-year-old American Indian secondary school adolescents.
In choosing this methodology, Flynn et al. argued that a phenomenological perspective offered a

49
practical approach to investigating the multifaceted issues, with consideration to the lived
experiences of the participants, their held meaning to it, and its relationships to varying
situations. Therefore, the use of a descriptive, phenomenological approach was appropriate for
this study, as it offered a significant advantage that enabled the creation of rich data necessary to
answer the research questions. This approach provided insights into the perceptions of SBMHCs’
views of mental health care within the school settings in a school district in Connecticut of the
United States.
To ensure that the perceptions of SBMHCs were uncovered, the 15 participants came
from a purposely selected school district in Connecticut. Also, open-ended, semistructured
interviews of SBMHCs enabled access to saturated data to answer the following questions.
RQ1: What do SBMHCs perceive as factors that may affect the use of SBMH services by
adolescents from a school district in Connecticut, United States?
RQ2: What do SBMHCs perceive as barriers meeting the mental health needs of
adolescents from school district in Connecticut, United States?
Role of Researcher
The role of the qualitative researcher as the instrument is to interview, code, and analyze
the investigative process to achieve accurate reflection of the research as it proceeds (Flynn et
al., 2013). In this study, my vision of the research process relied on my educational experience as
a novice researcher, former classification correctional counselor, mental health clinician; and a
former member of the Connecticut Department of Children and Families, integrated support
systems (ISS). These personal experiences provided an authentic and contextual understanding

50
of this study. The integrity of collected data, analysis, interpretation and conclusion of the study
are enhanced when the researcher’s credibility can be assured (Houghton, Shaw, & Murphy,
2012). For this study, injecting my personal values and bias was a concern. To prevent these
from becoming a limitation, I developed strategies, such as bracketing, to reduce the effects of
preconceiving notions. Bracketing refers to the proactive steps taken by the researcher to
minimize the inevitable transmission of personal values, interests, emotions, and theories into the
research process (Tufford & Newman,2010). Chang, Fung, and Chien (2013) suggested that
bracketing is recommended before data collection and analysis to ensure the validity of data and
unchanging in the meaning of the phenomenon under study. In addition, Gill, Stewart, Treasure,
and Chadwick (2008), recommended the following techniques:
1. Avoid the use of leading questions
2. Maintain neutral yet open body language
3. Record interview audio and take field notes
Prior to Walden University’s Institutional Review Board (IRB) approval, I requested
permission and subsequently received approval from the office of the school’s district
superintendent to contact school principals and solicit SBMHCs for their participation. The
solicitation process involved making direct calls using a directory (a public record) and sending
e-mails to purposefully selected schools in a school district in Connecticut. The demographics of
A School District in Connecticut (ASDCT) are as follows:
• Student population (Redacted)
• Sampling: (Redacted) elementary, middle, and high schools

51
• Demographics
• White
• Black
• Hispanics
• Asian Americans
• Other
None of the schools in the district, and thus none in the sample, differed significantly
from these figures. To recruit, I created a study flyer (Appendix E) to provide contact details for
the participants who met criteria set forth for this study. As an additional strategy to recruit
participants, I visited individual schools to drop off study flyers at a convenient designated
private mailbox for the counselors to volunteer and participate in my research. After receiving
12-15 SBMHCs' agreements to participate, face-face interviews commenced. This total number
of participants was chosen, as the significant concern in a study of this kind is saturation, or the
point at which continued data collection is unlikely to yield new information (Yin, 2013). A
sample size of 12-15 counselors was considered appropriate for the achievement of saturation
The counselors included in the sample were drawn from 13 purposely selected schools in the
district. Each school had varying number of counselors depending on capacity, resources, and
need.
The location of interviews varied according to individual participant's preference. Upon
completion of the interviews, I uploaded the audio interviews from a digital recorder to a
computer and created a file folder for the participants’ audio recordings that was only accessible

52
to me. With the same computer. I uploaded the interviews audio to a secure web link to a
professional transcriber for data transcription. Once interview transcripts were received, case
files were created for each participant for organizing and coding with NVivo software.
Additionally, conducting reviews of the salient literature of SBMH services was crucial for this
study. Qualitative research findings gain recognition when the researcher establishes trustworthy
procedures to show credibility, transferability, dependability, and confirmability (Flynn et al.,
2013; Tufford & Newman, 2010). To ensure that these principles were incorporated into this
study, decisions regarding the sample size, descriptive rigor, data collection, and analysis were
made in collaboration and with the support of my dissertation committee.
Methods
In this study, I used a descriptive, phenomenological, qualitative framework to explore
the perceptions of SBMHCs about factors affecting adolescents’ use of services. This
methodological framework enabled me to stay focused in gaining an understanding of the study
participants’ lived experiences and the meaning they assigned to various circumstances (Krose et
al., 2013). Additionally, my analysis of the SBMHCs’ perceptions relied on a phenomenological
framework because of its multidimensional nature and evolving ability to adapt to different
conditions. A descriptive phenomenology design provided the best lens for my study because it
offered me the flexibility, and the freedom for self-reflection when making critical decisions
required during the research process. The design helped me to uncover the essential components
of the lived experiences of SBMHCs.

53
Participant Selection Logic
The participants in this study were SBMHCs who worked fulltime at 32 to 40 hours per
week. The participants provided services to adolescents attending school in a school district in
Connecticut. A purposive sample of 15 SBMHCs in this study ensured that the data collected
reached saturation point. Although there is no consensus among methodologists on an ideal
sample size for qualitative research, some researchers have provided evidence for the use of
purposive sampling to select study participants (Cleary, Horsfall, & Hayter,2014; Gentles et al.,
2015). Guest, Bunce, and Johnson (2006) used 12 participants’ interview transcripts to reach data
saturation. Similarly, Lee, Landy, Wahoush, Khanlou, Liu, and Li (2014) used a descriptive
phenomenological approach to gain an understanding of the lived experiences of 15 immigrant
Chinese mothers to answer their study questions. For this research, obtaining information useful
for understanding the complexity, depth, variation, and context surrounding SBMHCs’
perceptions was imperative. Hence, I selected SBMHCs who had experienced working with
adolescents from a school district in Connecticut.
Criteria for Participation
In this study, SBMHCs who met the criteria for participation came from a purposely
selected school district, but from multiple schools, in a school district in Connecticut, based on
the following conditions:
1. Self-identified as a school-based professional (i.e., psychologist, school counselors,
social workers, special education teacher, and a nurses working in a school district in
Connecticut

54
2. Possess the ability to share honest personal assessment of school-based mental health
services’ challenges and discuss possible solutions
3. Demonstrate good knowledge of common mental health issues faced by adolescents
and an ability to describe thoughts in the English language
4. Consent to a 30- 45-minute interview
5. Must have 1 or more years of service experiences providing care in a school
counseling setting
6. Participant received an explanation of the purpose, risks, and benefits of the study.
7. Must agree and allow the interview to audiotape to enhance accuracy of data
collected
Instrumentation and Data Collection Procedures
For this study, collecting data through interviews was appropriate due to the historical
and cultural context of the phenomena of inquiry. The data collection consisted of procedures
that were sensitive to the cultural, legal, and ethical issues involved. Approval from Walden
University IRB, and consent from purposely selected SBMHCs from a school district in
Connecticut, were acquired before interviews were conducted (Appendix A). During this
process, I determined that the school districts had their own approval procedures that should be
followed. In this case, I applied and obtained the district level approval prior to application for
approval to Walden University. The district approvals were attached to the Walden University
approval request submission to meet the requirements of the university. The interviewing process
involved open-ended questions for data collection and handling, and the principles stipulated in

55
the National Institutes of Health protecting research participants’ consents guided this process
(Appendix B). The guideline emphasizes the overarching themes of respect for persons,
beneficence, and justice (U.S. Department of Health and Human Service, 2014). Protecting the
identity and individual participants’ confidentiality was a component of this study process.
Data collection activities ensured accurate and unbiased information to help establish
credibility, transferability, and confirmability. The types of data collected included interviews
(open-ended interview transcripts). To ensure that the interview questions were appropriate and
addressed the phenomena under study, I sought out my dissertation committee in refining and
assessing the degree of bias in framing questions, collecting background information, adapting
research procedures stipulated in dissertation guidelines, and using Walden University research
resources. I ensured that the developed research questions (Appendix B) met the quality criteria
for this study. I used two participants to conduct a pilot study of the interview protocol,
recruitment strategies, and effectiveness of audiotape instrument in capturing the essence of the
lived experiences of SBMHCs. Hilton (2015) highlighted the importance and use of a pretest to
check if research tools work as intended with participants' understanding.
The interview protocol for this study had contents such as title, time of interview, date,
location of interview, interviewer, interviewee, the profession of the interviewee, and a brief
description of the study. I ensured that the management of data collected abided by the standards
set by Walden University IRB and National Institute of Health regarding participant’s
confidentiality (Appendix A). The following techniques facilitated the management of data
collected:

56
1. Participant list was secured using a password-protected file with a backup file.
2. A master list of types of information gathered maintained and protected the anonymity of
participants by masking their names in the data.
3. A data collection matrix served as a visual means of locating and identifying information
for the study.
Different methods, including NVivo 10 version, helped to organize collected data to
enhance data control procedures and their reliability. First, I created a database to contain an
identifier for each participant in the dataset. Second, I listed information in one row of the
database instead of multiple places. Finally, I included participants’ transcribed interview
responses to avoid entering incorrect information.
Issue of Trustworthiness
The study of SBMHCs’ perceptions must meet a threshold of quality, trustworthiness,
and credibility to achieve its objectives. Houghton et al. (2012) described qualitative research as
an artistic expression to assessing data quality. The quality of the research process is essential for
interpretation of data collected and the conclusion. To demonstrate the rigor of this research
process, I used the below discussed processes to ensure credibility, transferability, dependability,
and confirmability.
Credibility
The credibility of the researcher is a consideration when users of research assess the
value and believability of findings (Koch, 1994). To enhance the credibility of this study, I
established prolonged engagement through frequent visits to purposely selected schools to gain a

57
full understanding of SBMH services. In addition, I used multiple sources of data including field
notes, memos, audio, and relevant literature to analyze the data gathered by triangulation. Cleary
et al. (2014) and Tufford and Newman (2012) asserted that the use of a triangulation technique
helps the researcher to validate data by verification using multiple sources. I made sure to
implement frequent contacts with my study mentor throughout the time of this study.
Additionally, I consulted with my dissertation committee, and posted limited information about
the research in the discussion board for peers’ comments and reviews of the research process as
an additional external check.
Transferability
To ensure transferability of SBMH study findings, I used thick description strategies to
provide adequate details of the research context for the reader. According to Koch (1994), this
technique allows the researcher to make an educated determination of the transferability of the
conclusions to their context. These strategies included detailed accounts of methods used, and
appropriate use of SBMHCs quotations from interview transcripts to allow for alternative
interpretations by readers.
Dependability
The concept of reliability was an essential element for assuring trustworthiness in
qualitative research (Houghton et al., 2013). To establish the dependability of my study findings,
I implemented two strategies: audit trail and use of reflexivity. The use of audit trail enabled me
to review the decisions I made in this research process and explained the rationale for the reader
to discern the methodological and interpretative approach used. Houghton et al. (2013) suggested

58
that users of research findings must assess the process in which conclusions are reached to
provide a detailed account recognizable to the readers. Another aspect of the audit trail strategy
involved the use of NVivo software to run three specific queries (text search, coding, and matrix)
to provide a comprehensive tracking of decisions made during data collection, the sufficiency of
identified concepts, and the dependability of participants’ context.
The final strategies used to ensure dependability of this study was the use of the
reflexivity strategy to enhance my self-awareness throughout the research process. I maintained a
reflective diary during this investigation on the decisions I made, their rationale, my senses, and
personal challenges conducting this research. Researchers Jootun, McGhee, and Marland (2009)
posited that reflexive account provides a history of the researcher, their interests, and how
theoretical perspectives influenced data collection and research.
Conformability
The process of establishing dependability and conformability are similar (Houghton et
al., 2013), I used the same audit trail strategy to achieve conformability of study findings. I
documented decisions made regarding methodology and data interpretation. I used NVivo
software to run different queries to audit research conclusions and eliminate redundancy in my
arguments. Running different queries also helped me to check or confirm the propositions I made
from the interview transcripts (Koch, 1994). Recognizing the importance of using reflexivity to
enhance qualitative research conformability, I maintained a journal to document all decisions
regarding data interpretation to reduce bias resulting from unacknowledged assumptions.

59
Data Analysis Plan
The analysis of SBMHCs perceptions involved using the data analysis software NVivo,
to organize data into a list of statements. Colaizzi’s 6-steps of data analysis techniques was used
to facilitate the description of individual thoughts and experiences of SBMHCs (Gill & Fazi,
2013). Colaizzi’s 6-steps constructs guiding the data analysis of SBMHCs’ perceptions are listed
below.
1. The accuracy of transcript contents was verified against the recorded interviews. Then
case files of interview transcripts were uploaded to NVivo software.
2. For each transcript, NVivo was used to identify relevant statements guided by the
research questions about adolescents’ use of SBMH services as narrated by SBMHCs.
3. Defined relevant statements identified by NVivo was interpreted guided by the
research questions from each participant’s interview transcript.
4. NVivo software was used to sort relevant statements into categories, clusters of ideas
and themes.
5. The perceptions of SBMHCs about adolescent use of SBMH services was summarized
to develop an exhaustive report on the studied phenomenon.
6. With the development of an exhaustive description in step 5, SBMH services structure
was constructed, using SBMHCs' perceptions to identify reasons why adolescents from
a school district in Connecticut, United States are not using services.

60
Ethical Considerations
Ethical consideration must be upheld in all social science research process to guide
against potential threats to human subjects (NIH, 2015). The procedures set forth for this study
meets the Walden University IRB and the National Institutes of Health (NIH) Research
Standards. These rules espouse core principles such as respect for persons, beneficence, and
justice (NIH, 2015). The ASCA (2015) and the NASP (2015) maintain ethical standards required
of its members. The study of SBMHCs’ perceptions involved human subjects; therefore,
ensuring that participants are valued, and care taken to protect and maintain their confidentiality
was essential (Appendix A). To this end, I have followed all applicable laws including obtaining
the consent of participants (Appendix A) without the use of undue influence.
Summary
A qualitative descriptive phenomenology was appropriate for exploring SBMHCs’(SBMHCs)
perceptions of factors affecting disparities in adolescents’ use of SBMH services. The chapter
provided details of the research process, including research design and rationale, my role as the
sole investigator, criteria for participation; number of participants, data collection procedures,
issues of trust, a data analysis plan, ethical considerations, and summary. Chapter 4 contains the
discussion about the data collection process, SBMHCs data analysis concept map, the
participants profile table, Flow chart of semi-structured interview questions used for this study;
data analysis, and the findings. In addition, the chapter included individual SBMHCs’ comments
about their perceptions of adolescents, use of SBMH services to identify themes for codes.

61
Chapter 4: Results
Introduction
The purpose of this descriptive, phenomenological study was to examine the perceptions
of SBMHCs about factors affecting the use of SBMHS by adolescents from a school district in
Connecticut, United States. The participants were selected because SBMHCs are, by the nature
of their professions are the first responders in identifying adolescents’ mental health needs.
SBMHCs perform different functions, including mental health assessments, prevention,
intervention, and referrals, while focusing on how mental health affects learning and ensures
academic success for adolescents with identified behavior problems (ASCA, 2015). Fifteen
participants from purposely selected schools volunteered and participated in this study. The
following research questions were the research questions that guided this study:
RQ1: What do SBMHCs perceive as factors that may affect the use of SBMH services by
adolescents from a school district in Connecticut, United States?
RQ2: What do SBMHCs perceive as barriers meeting the mental health needs of
adolescents from a school district in Connecticut, United States?
The two research questions served as a guide in the interview process that enabled me as
the sole investigator to capture the lived experiences of SBMHCs, gain increased knowledge,
and obtain a detailed understanding of the phenomenon of factors and barriers affecting the use
of SBMH services by adolescents from a school district in Connecticut. This chapter includes the
participants’ profile table, data collection, concept map, flow chart of semistructured interview
questions, data analysis, and results. This chapter will end with a summary.

62
Pilot Study
Before the final submission of the IRB ethics forms review, I applied and received
copyright permission to use two validated interview questions used in a similar study by Gamble
and Lambros (2014, Appendix B2) in Los Angeles and Orange County schools, California,
United States. To ensure that the questions were appropriate for this study, the interview protocol
used with SBMHCs was developed from the same researchers (Gamble & Lambros,2014). The
interview questions were analyzed via item response design, and the protocol was updated with
more explicit directions. Four semistructured, open-ended questions that were identical and
purposely designed and three follow-up questions were asked. According to Mertens (2010),
qualitative interviews provide a forum to uncover the participants’ subjective interpretations of
social phenomenon, opinions, experiences, and collective understandings.
After receiving IRB approval# 12-21-17-0409877, two school principals from the school
district were contacted about the study and gave permission to contact two SBMHCs from the
school district for the pilot study. The two participants were purposely selected and who met the
eligibility selection criteria designed for the actual study agreed to participate and completed the
pilot study. The purpose of the pilot study was to test the interview protocol, recruitment
strategies, and effectiveness of audiotaping to capture the lived experiences of SBMHCs. The
pilot study enhanced my research skills as a student researcher on three skill sets: (a) the ability
to identify problems and barriers related to research; (b) the ability to assess acceptability of
interview protocols; (c) the ability to determine the scope, validity, and method of the research
process (Janghorban, Roudsari, & Taghipour, 2014). Through the pilot study, I was able to

63
evaluate the problems and challenges when I conduct the large-scale version of my study. I was
able to determine whether the interview protocol was effective in gathering information needed
to answer the research questions. Moreover, I was able to define the scope of my research more
clearly because of the pilot study.
Study Setting
The participants’ responses to interview questions formed the only source of data used in
the study. Face-to-face interviews were conducted with each participant in a private room in a
public building of his or her choice and to make the participants feel more comfortable in sharing
their experiences. The location and decision for each interview was focused on protecting the
identity and confidentiality of the participants. Each participant and I agreed to the location,
date, and time for interview in a private room under study setting in a public building. There
were also gaps between the interviews of the participants so that they would not see one another.
The Participants Profiles with Limited Demographic Information
The 15 SBMHCs met the following eligibility criteria:
1. Self-identified as a school-based mental health professional (i.e., psychologist, school
counselor, social workers, special education teacher and nurses, and working in the
school counseling setting in a school district in Connecticut, United States
2. Possess the ability to share honest personal assessment of school-based mental health
services’ challenges and discuss possible solutions
3. Demonstrate good knowledge of common mental health issues faced by adolescents
and an ability to describe thoughts in the English language

64
4. Consent to a 30- 45-minute interview
5. Must have 1 or more years of service experiences providing care in a school
counseling setting
6. Participant received an explanation of the purpose, risks, and benefits of the study
7. Must agree and allow the interview to audiotape to enhance accuracy of data
collected
Below is the brief description (see Table 1) of the role and work experiences of the 15
SBMHCs. The participants in this study were assigned pseudo names to protect their identity.
Each profile provided details about the work of each participant and how they interacted with
students.

65
Table 1
Participant Demographic Profile
Participants
(Pseudo- names)
Job Title (in addition to
School Counselor)
Years of Experience Summary of Role and Work with
Students
Alicia Special Education 5 Provides, individual and group counseling
and teaches social studies for seventh and
eighth grade students
Anna Assistant Principal 15 Counselor oversees the counseling
department and supports students in
academic, social and emotional wellbeing
Barbara School Counselor 20 Provides counseling for K8-12 students
for their socio-emotional, academic,
individual and family groups
Debra School Counselor 2 Counseling, former teacher deals with
mostly mental health of the students.
Diva School Counselor 1 Counseling, former Social work
supervisor provides individual and group
sessions with students.
Joy School Counselor 4 Counseling, former teacher for K-8
students provides individual and group
counseling.
Julie School Counselor 4 Counselor provides individual counseling
and make referrals to other professionals
Madonna School Counselor 3 Provides in-classroom lessons that are
non-academic based. For example,
provides group counseling that focused on
the need for the students such as divorce,
friendship, or bullying
Maria School Counselor 3 Works with students from ninth to twelfth
grade whose English is their second
language and provides referrals when they
cannot meet the needs of the students
Maya Social Worker 20 provides social work services and
counseling for social and emotional
wellbeing of adolescents ages 14 - 21
Opera School Nurse 4 Former nurse for children ages 13-17 and
families in a hospital setting. Provides
medical and mental health assessments
and make referrals to other professionals
Sophia School Counselor 9 Counseling providing emotional, social
and academic support; college, career and
future planning
Sotomayor School Psychologist 3 Psychologist provides psychoeducational
testing, individual, and group counseling
Terry Special Education 2 Teaches social studies and English,
provides services to students with
emotional and social needs
Wilbur School Principal 5 Provides individual counseling that,
includes, tutoring, social, emotional
support, and college support services

66
Data Collection
The interviews involved the use of four semistructured, open-ended questions with three
follow-up questions for data collection:
IQ1. Please describe your role and work experiences in providing services to adolescents
in the school setting.
Follow-up question: What barriers do you perceive affect best outcomes for adolescents
at-risk?
IQ2. Based on your experiences, who most often receive SBMHS and why?
Follow-up question: Are there any other types of services delivered frequently?
IQ3.In your opinion, what do you think motivates the adolescents to use these services? How do
you motivate adolescents with mental health needs to use these services?
Follow-up question: Do you have a specific way of identifying these adolescents in
need?
IQ4. Please describe the factors you attribute to lack of SBMHS use by some
adolescents.
Hilton (2015) highlighted the importance and use of a pretest to check if research tools
work as intended with participants' understanding. Both the dissertation committee and Walden
University’s IRB approved of the data collection tool. These questions were also validated in the
pilot study.
During the interviews, open-ended questions were used to understand SBMHCs’
perceptions about factors that affect the use of SBMH services by adolescents from a school

67
district in Connecticut, United States. The interviews took place in a private room at a public
location of the participants’ choice. A private setting assured the confidentiality and privacy of
the participants and the information shared in the interviews. Each interview lasted between 30
to 45 minutes, where participants shared their experiences as SBMH service providers to
adolescents.
After completing the interviews, the files were uploaded from a Sony ICD-UX533 digital
recorder to a password-protected file folder on the computer. Then I contracted a professional
data transcriber who signed a confidentiality agreement to protect the anonymity of the interview
participants (Appendix G). With the same computer, interview recording files were shared with
the transcriber via a secure web link. Once all transcripts were received in MS Word, duplicate
copies of the transcribed data were stored on the computer and on password-protected external
storage devices to avoid data loss, in case of accidents or unexpected technological failure.
Data Analysis
The analysis of SBMHCs’ perceptions involved using the computer-assisted data analysis
software NVivo to organize data into a list of statements. The use of Colaizzi’s 6 steps of data
analysis facilitated the description of individual thoughts and experiences of SBMHCs (Gill &
Fazi, 2013). Colaizzi’s approach to data analysis enhances rigor and provides the researcher
access to unspoken and categorical meanings embedded in the lived experiences of the study
participants (Edward & Welch, 2011; Yilmaz, 2013). According to Suryani (2016), The
synthesis of the researcher’s own reflection and the plurality of subjects are what underpin

68
Colaizzi’s steps for data collection and analysis. In this study, Colaizzi’s 6-steps guided the data
analysis of SBMHCs’ perceptions are as listed below:
1. The recorded interviews for this study were transcribed by a professional transcriber. In
keeping with Step 1 of Colaizzi’s 6 steps, I reviewed a few transcripts to conceptualize
the phenomena of SBMH services before importing case files of interview transcripts into
NVivo software.
2. For each transcript, NVivo software was used to identified relevant statements about
adolescents’ use of SBMH services as narrated by SBMHCs.
3. Multiple source of data gathered by triangulation was used to interpret and define
significant statements identified by NVivo from each participant interview transcript.
4. NVivo was used to organize relevant statements into categories, clusters of ideas, and
themes.
5. With this step, identified themes by NVivo were combined into the description of the
textures of SBMHCs experience, and the exhaustive explanations were supported with
quotations from the transcripts. Colaizzi (1973) posited that in writing a thorough
description of the phenomenon, the researcher should integrate information related to the
phenomenon of inquiry.
6. After achieving a thorough description with Step 5, the fundamental structure of SBMH
services was constructed. This process involved reviewing the exhaustive description,
themes, and subthemes identified by NVivo reflective of SBMHCs' perceptions to

69
identify reasons why adolescents from a school district in Connecticut. are not using
services
7. This step was not used because it would be time consuming for the participants. Giorgi
(2008) identified a theoretical reason for not using this step; phenomenological method,
properly employed results in eidetic findings that can only be checked by
phenomenological approach that may not be known by the participants. Alternatively, the
strategy of using cross verification of the interview transcripts contents against the
recorded interviews was implemented. Also, the use of follow-up questions and asking
the participant to restate or clarify comments during the interviews, and using a
professional transcriber, contributed in assuring the validity of transcripts and audio
recordings.
Evidence of Trustworthiness
Credibility
To ensure the credibility of the study, I established prolonged engagement through
frequent visits to purposely selected schools to gain a full understanding of SBMH services. I
also used multiple sources of data including audio and relevant literature to analyze the data
gathered by triangulation. Implemented peer review, using bi-weekly consultation with my
dissertation Chair for feedback and as an additional external check.
Transferability
To ensure transferability of SBMHCs’ study findings, I used thick description strategies
to provide adequate details of the research context for the reader. Thick description refers to

70
writing practices that qualitative researchers use to explain cultural context or lived experiences
of people and the meaning they attach to their actions or expressions (Bandenhorst, 2016) Thin
descriptions make statements without meaning or relevance. Thick description strategies that I
used included not only describing and observation but also the context in which that behavior
occurred. According to Koch (1994), this technique enables the researcher to make an educated
determination of the transferability of the conclusions to their context. In this study, I provided
detailed accounts of methods used and appropriate use of SBMHCs’ quotations from interview
transcripts to allow alternative interpretations by readers.
Dependability
The concept of dependability is a component for assuring trustworthiness in qualitative
research (Houghton et al., 2013). Dependability refers to the validity of the process or the
measures taken by a researcher to authenticate that study findings are systematic, objective, and
repeatable. To establish dependability of SBMHCs’ study findings, I implemented four
strategies: (a) I used bracketing that are guided by the thinking activity of reflexivity (Chan,
2013) to minimize potential effects of my personal values, experiences, or preconceived notions
on the research process and to demonstrate the validity of data collected and the analysis of this
study; (b) I used the approved research methodology and IRB consent form as a systematic guide
for this study; (c) I used four semistructured interview questions with three follow-up questions
that was approved by the committee and validated by a pilot study for this research; (d) I used an
audit trail to track the decisions that I made while using NVivo software to run queries (text
search, coding, and matrix),and to extract verbatim statements of SBMHCs that provided

71
sufficiency of identified concepts and dependability of the participants’ context. The use of audit
trail allowed me to explain the rationale for the reader to determine the methodological and
interpretative approach used. Also, using reflexivity as a strategy enhanced my self-awareness
required throughout the research process. Maintaining a reflective diary during this investigation
helped with the decisions made, their rationale, the senses, and the personal challenges
conducting this research. According to Jootun et al. (2009), a reflexive account provides a
history of the researcher, his or her interests, and how theoretical perspectives influenced data
collection and research.
Conformability
The same audit trail strategy and the rigorousness of this research method helped to
achieve conformability of the results through the evaluation of the decisions I made regarding
methodology and data interpretation was appropriately documented. Additionally, maintaining a
journal facilitated all documentation decisions regarding data interpretation to reduce bias
resulting from unacknowledged assumptions (Bergin, 2011 & Miles et al, 2014).
Results
Each participant was interviewed privately on the scheduled date and time at their
preferred interview setting in a private room in a public building. After the interviews, the
recordings of the interviews were uploaded to a password protected computer laptop and
organized into individual files I uploaded to a secure web link to a contracted professional
transcriber with a confidentiality agreement (Appendix H) for data transcription. Once interview
transcripts were received, I made copies for documentation into a study file folder and saved
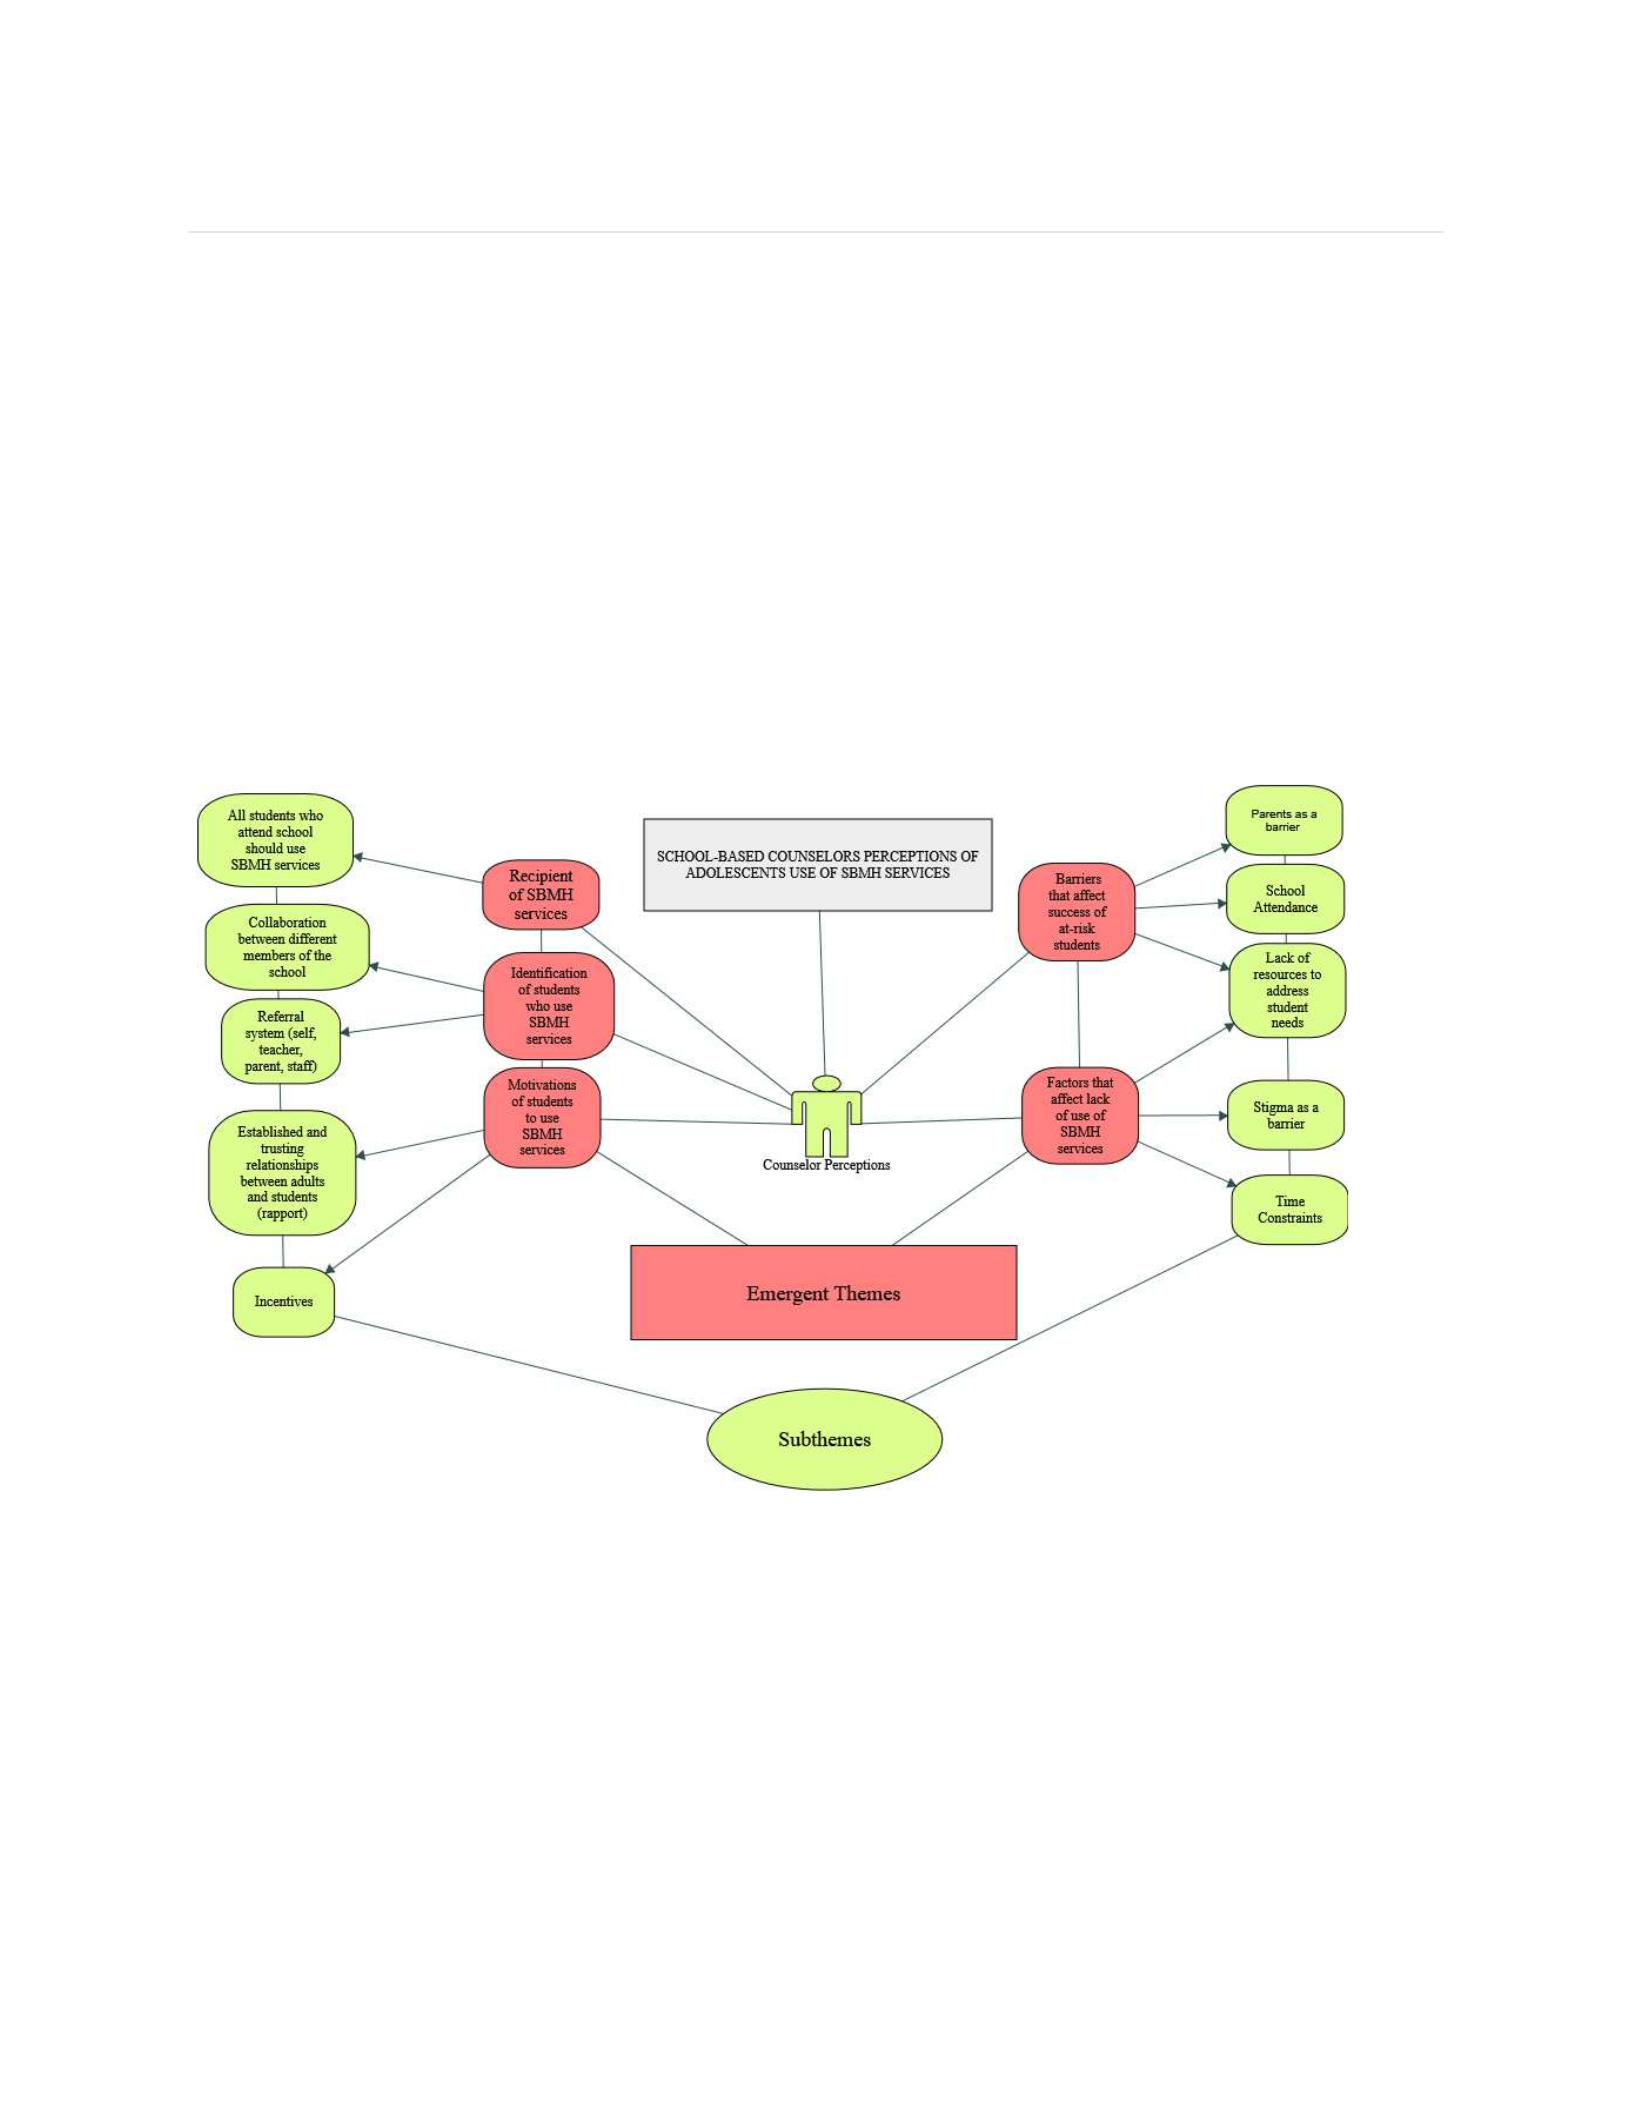
72
individual participant’s transcripts to a password protected cases folder only accessible to me. to
be imported from the computer into NVivo to perform different activities including coding to
identify, organize themes and extracting examples of verbatim sentences to provide an exact
depiction of experiences of the participants as narrated by the study participants during
interviews for analysis. There were five major themes that emerged from the data analysis.
Three themes answered the first research question. Two themes answered the second research
question.
Figure 1. Relationship between themes and subthemes of SBMHCs perceptions

73
All the participants answered all the interview questions. After each interview, I thanked
the participant for their participation, and asked if they had any question for me. Some of the
participants asked some questions regarding the study and I politely answered their questions.
RQ1: What do SBMHCs perceive as factors that may affect the use of SBMH services by
adolescents from a school district in Connecticut United States.?
The first research question was about the factors that may affect the use of SBMH
services by adolescents from a school district in Connecticut, United States. To generate quality
responses, I made sure that all the participants are active SBMHCs from a school district in
Connecticut. To achieve this goal, I developed four semistructured interview questions (IQs)
with three follow up questions that were answered by the participants: The rational to use semi-
structured and follow up questions for the interviews was specific to achieving three goals: a) To
vary the questions to generate rich data to answer the research questions, b) To enhance
descriptive rigor and demonstrate validity required for this study context for the reader to
decipher and c) To establish that the procedures used for this study was consistent, systematic,
unbiassed and repeatable. Below are the interviews questions and flow chart for visual clarity.
IQ1. Please describe your role and work experiences in providing services to adolescents in
the school setting.
Follow up question: What barriers do you perceive affect best outcomes for adolescents at-
risk?
IQ2. Based on your experiences, who most often receive School-based mental health
services (SBMHS) and why?

74
Follow up question: Are there any other types of services delivered frequently?
IQ3.In your opinion, what do you think motivates the adolescents to use these services? How
do you motivate adolescents with mental health needs to use these services?
Follow up Question: Do you have a specific way of identifying these adolescents in need?
IQ4. Please describe the factors you attribute to lack of SBMHS use by some adolescents?
75
Figure 2. Interview questions flow chart
All SBMHCs revealed perceived factors and barriers that may affect the use of SBMH
services by adolescents from a school district in Connecticut, United States. Two main themes
emerged from participant responses to RQ1: (a) identification of students who use SBMH
services and (b) motivations of students to use SBMH services. Table 2 summarized the themes
and subthemes that emerged from participant responses.
IQ1 FOLLOW
UP:
What barriers do
you perceive
affect best
outcomes for
adolescents at-
risk?
IQ2 FOLLOW
UP:
Are there any
other types of
services
delivered
frequently?
IQ3 FOLLOW
UP:
Do you have a
specific way of
identifying these
adolescents in
need?
IQ1:
Please describe
your role and
work experiences
in providing
services to
adolescents in the
school setting.
IQ2:
Based on your
experiences,
who most often
receive School-
based mental
health services
(SBMHS) and
why?
IQ3:
In your opinion,
what do you think
motivates the
adolescents to use
these services? How
do you motivate
adolescents with
mental health needs
to use these services?
IQ4:
Please describe
the factors you
attribute to lack
of SBMHS use
by some
adolescents?

76
Table 2
Emergent Themes, Response Frequency and Subthemes for Research Question 1
Research Question Themes Resp
Freq
Subthemes
RQ1: What do SBMHCs perceive as
factors that may affect the use of SBMH
services by adolescents from a school
district in Connecticut, United States?
Theme 1. Identification of students
who use SBMH services
Theme 3. Motivations of students
to use SBMH services
7
7
6
6
Theme 1 Subtheme 1. Referral system
(self-referral, teacher referral, parent
referral, staff referral)
Theme 1 Subtheme 2. Academic data
(grades and attendance)
Theme 2 Subtheme 1. Established and
trusting relationship) (rapport)
Theme 2 Subtheme 2. Incentives
Theme 1. Identification of students who use SBMH services
Identification of students who use SBMH services also indicated some factors that
influence students’ use of SBMH services. I was interested to know how the participants
identified students who might benefit from using SBMH services. The rationale behind this
question was whether their schools have a framework that would make it easier for students who
need SBMH services to be identified and to have access to SBMH services. All participants
recognized that each school might have a different process and different members of the
committee or groups that identifies students who need SBMH services. Although there were
different programs, two types of structure were identified on how to identify students in need of
SBMH services. There were two subthemes that emerged from this theme: collaboration between
different members of the school and different referral systems in place at the school.

77
Collaboration between different members of the school. Some of the participants
identified programs where students and staff collaborate to identify students who might need
SBMH services. Alicia mentioned that each school has their own system for identifying students
who might benefit from SBMH services. In her school, they have RBI and SSST. She added:
We have the SSST if they have something about the behavioral or something like that.
We start the process to help the student – SSST is a staff – student team – we meet and
discuss the student behavior and, try to help the student to find different strategies, to
work with them. If that doesn’t work, we refer to the SRBI. SRBI is another process to
get the student to – it’s a process to get the student to get a PPT, a meeting about special
ed services.
Maria has a similar set-up at her school. They form a group of people who are members
of the school and hold meetings during Monday mornings. This group is composed of school
counselors, the special education teacher, an administrator, and a social worker. She described
what goes on these meetings:
We’ll sit down and discuss cases that have been referred to us by teachers, by other
students, referrals that we ourselves bring out, and we discuss those students. The
purposes of those meetings are so that we can put interventions in place and if those
interventions don’t work, then we ‘level it up.’ But that is the first level of how we
identify students that most likely will need some sort of intervention; whether it be
mental health, academic. A lot of the times, we find that those students need some sort of
counseling.

78
In Joy’s school, they have created advisory groups. Joy provided a detailed process on
how these advisory groups work. Joy shared that the students have to feel that they can come to
at least one person if they need to talk or help. The advisory groups were created to address this
goal. Joy stated:
Every teacher will have a go-to person. So, everyone, every teacher, whether it be
teacher, principal – every staff member will have ten students that they will meet with
twice a month, in order that they can build rapport, so that we can have a better gauge of
what is going on with our population. But the way I do it, we have assemblies to find out
what is going on with our students; we also have one-to-one meetings – it takes a lot of
work to organize, but we have frequent meetings with our students and I have an open-
door policy, so that if they need me, I’m available to them.
Different referral systems. Several types of referral were named by the participants to
identify students who use SBMH services. Most of the schools have a holistic or team approach
in terms of identification of students who need SBMH services. Any individual (student,
teacher, staff, parent, or external agency) may refer a student to a team usually composed of staff
and students. This team will meet and discuss the facts of the case and will decide what will
happen to the student.
Alicia mentioned that they have SSST, a student-staff team, in their school. After
recommendation from the SSST, appropriate services are given to the student. If this does not
work out, then the student is referred to another program. Alicia shared:

79
we meet and discuss the student behavior and, try to help the student to find different
strategies, to work with them. If that doesn’t work, we refer to the SRBI. SRBI is
another process to get the student to – it’s a process to get the student to get a PPT, a
meeting about special ed services. But it’s a process. We start with the SSST and then
the SRBI and then we move to the special ed services.
Joy has a more personal approach in identification of students together with a team
approach. Joy makes it a point to establish good rapport with the students. Based from her
experience, a team is the best approach in identifying students who need SBMH services because
the students need to know that they can approach any member of the team if they are
experiencing difficulties in any aspect of their lives. Joy stated:
There has to be at least one person that they could come to. It doesn’t have to be me,
personally, but it could be the principal. And what we decided to do, in order to identify
the needs of the students, we have created, recently, advisory groups so every teacher will
have a go-to person. So, everyone, every teacher, whether it be teacher, principal – every
staff member will have ten students that they will meet with twice a month, in order that
they can build rapport, so that we can have a better gauge of what is going on with our
population. But the way I do it, we have assemblies to find out what is going on with our
students; we also have one-to-one meetings – it takes a lot of work to organize, but we
have frequent meetings with our students and I have an open-door policy, so that if they
need me, I’m available to them.

80
Joy also added that the students should feel that the person or any member of the team
should make himself or herself become available. They have to meet with the individual and
find out how they are coping with their life. Most importantly, Joy also mentioned that parental
involvement is important of the process.
Maria shared how her academy addresses the identification of students who need SBMH
services. They have child study meetings. It is composed of various members of the academy.
Maria specified:
We have something called child study meetings. They usually take place Monday
mornings, and it’s a group of people from the academy, leaders from the academy, so at
the academy meetings it will be the school counselors, the special ed teacher, an
administrator, and a social worker, and we’ll sit down and discuss cases that have been
referred to us by teachers, by other students, referrals that we ourselves bring out, and we
discuss those students. The purposes of those meetings are so that we can put
interventions in place and if those interventions don’t work, then we ‘level it up.’ But
that is the first level of how we identify students that most likely will need some sort of
intervention; whether it be mental health, academic. A lot of the times, we find that those
students need some sort of counseling.
Maya emphasized the need of working in a team so that a student will not slip through
the cracks. Another advantage of working in teams is that students will not be forced to go to
only one professional, they can choose from any member who they want to talk to. Maya further
explained:

81
We work as a team. So, if I miss something, through a crack, that’s what the team is for.
Because, what a student won’t tell me, a student will tell another team member. And
everybody knows that everything that comes in that’s at-risk, comes to the social worker.
If I don’t get it, I get it from a team member. Somewhere along the line, someone will
tell me. So, either a student will tell me – because people talk around here. When
something’s not right, it’s in the air. And you get to know your students, so you know
when things are off. I know when things are off with my students, because I know them.
And if I miss that mark, I got staff members that will bring me stuff, that if they’re not
talking to me they’re talking to staff members. And then I also have students that will tell
me stuff.
Most of the referrals are from teachers and other staff members of the school community.
Teacher referrals are common because teachers spend a lot of time with students inside the
classroom. Anna stated that most of the students who come to her office were referred by the
teachers. She observed:
So, they’re – a lot of them are pre-identified, as most of the teachers will just say to me,
“she’s just not right” or, we’ll use the name Johnny – “Johnny was a great student and
now he’s failing everything. I don’t know what’s wrong, but something’s wrong.”
Sophia shared that most of the referrals are from teachers. Teachers usually refer
students to SMBH services when they are falling behind in class or when they disrupt the class
due to bad behavior. In addition to teacher referrals, Sophia also mentioned that self-referrals are
also common instances in the process. Sophia stated:

82
Yes. So, depends on the need. But, if it’s an academic need, we have a tiered approach
of how, when students are starting to fall behind, they’re referred by the teacher and then
it’s a team of us that meet and identify what the need is and address it there. It’s very
similar also if it’s social or emotional, but then I have a lot of self-referrals, because I
believe the students know me now, and they have rapport with me, and they may say to
their friend that’s feeling sad and be like, ‘oh, you need to go talk to Miss Sophia.’
That’s how that goes. So, it varies. But yes, we have systems in place and then there’s
also referrals from family and students.
Students also interact with other individuals outside the classroom. Concerned staff of
the school community also refer students to use SBMH services. Anna, Barbara, and Madonna
mentioned that some students they provided services to were referred by members of the staff.
Wilbur has a more personal approach to the referral of staff members:
We literally train the staff to look for students who are in trauma. We really encourage
the staff to build relationships; I think that’s what is the key in education with students.
They’re not going to care until they know how much you care. A lot of times, most of
the students that we identify are through trauma. And, of course, we look at data. If we
have x student who was doing well in school and then all of a sudden –
Theme 2. Motivations of students to use SBMH services
The motivations of students to use SBMH services revealed factors that will influence
them to use SBMH services. When this question was asked, most of the participants answered
that trust was an important factor in motivating students to use SBMH services, especially to

83
students who will benefit from using the services. The development and maintenance of
relationships between SBMH service providers and the students were dominant in the answers of
the participants. There are two subthemes that emerged for this major theme: established and
trusting relationships between adults and students and incentive program.
Established and trusting relationships. Most participants stated that students use
SMBH services at their school because of well-established and trusting relationships between the
professionals and the students. Trust was also a prevalent concept. When students trust their
teachers or other adults in school, they will be able to come and talk to the adult about their
problems and needs. Most of the participants also mentioned that students talk to one another, so
it is important that the students know that they can trust the professional or else no one will use
the SMBH services anymore.
Anna mentioned that well-established, trusting relationships motivate students to use
SMBH services. She has been in her current position for 15 years and the students know that she
only breaks their trust when it is required by the law. Anna shared:
Students talk to each other; peer interaction is much more impressionable than people
think, and if someone goes to Miss Anna and Miss Anna helps them and doesn’t judge
them or hold it against them, or repeat it, more students will come talk to Miss Anna.
Debra emphasized the need to create connections with the student population. She
added:
I think it’s the people providing the services trying to find the way that connects with a
particular student and we have our school social worker who does, maybe, deep work

84
with students and then myself, who does maybe more of the work related to school
success and academics and getting through the day.
Julie talked about ensuring that there is trust so that the students know they are safe.
Opera also shared the same sentiment that students will usually approach the individuals they
trust. Julie also added the advantages of being accessible to the students. She stated:
I feel like it’s motivated by trust and knowing that we are safe individuals to come and
talk to. I think, in our role in particular, me and my colleague, that we’re a little more
accessible to students than my other colleagues that are in a different part of the building,
because we’re in the actual hallway.
Similarly, Terry mentioned that she does not exactly know what motivates the students.
However, knowing that someone is there for them helps these students. She added “but just
having someone there and they know that they’re there, I think motivates them. Having easy
access to these people definitely helps”. Sotomayor also has the same opinion regarding the
motivation to use SBMH services. He made himself visible to the students and connected with
them to ensure that they know that they have somebody they can talk to.
Maria mentioned the culture of the school. In their school, they are pro-mental health.
The SBMH employees go inside each classroom to explain their roles and to connect with the
students so that they will not hesitate to approach them. Furthermore, Maria mentioned that they
discuss that their main role is to create an atmosphere of discourse in anything that the student is
experiencing.

85
Sophia resonated the experiences of the other participants. She stresses the need for
relationships. She explained:
I think building relationships with the students, going into the classrooms, being a
friendly face, letting them know that you’re there, letting them know what you can
provide them; not just being a lady in the office, I’m in the building, I go into the
classrooms, I introduce myself, I let the students know why I’m here, what I want to offer
them. Just being involved and engaged with them so that they know who I am and being
comfortable and familiar so that when they have an issue or if they have an issue, they
know where to go and how to access that. That’s worked for me, and I believe the
students access me when they need to.
Aside from developing and maintaining relationships, the participants also mentioned an
incentive program. For some schools, they have incentives to motivate students to use SBMH
services. The participants who mentioned this incentive program works at schools that have a lot
of at-risk students.
Alicia mentioned that teachers try to motivate the students to use SBMH services. They
either give a prize or use good words to motivate the students. One of the incentives they
provide is technology. Alicia stated:
Well… this generation is – they like to use technologies and different things, and
probably we can give a privilege if they do something good in the classroom. We
motivate using the technology or something that they can create something. Or they can

86
participate in a program if they behave. For example, we have a safety patrol over here,
and we try to incentivize the students that make good decisions
Diva also shared a similar program in their school. For instance, students have to
maintain a certain grade point average to be able to play sports. They also have a Gold Card and
White Sheet. Diva further explained:
…when they reach a certain level, they get some incentives to be able to play ball, to be
able to go to a store. We have a store, we have a snack shop, we take them out on trips.
But for a couple of the boys, I think, that have really challenging behaviors, is the fact
that they get to play ball. If their grades aren’t up to par, if their behavior isn’t up to par,
they’re not going to be able to play. And that, really, when they hear that they might not
be able to play on Wednesday, that really take them to really thing about it. Because
that’s their passion. For a lot of the kids, they think ‘this is my way out.’ So, you take
that from them, they feel lost. So, it’s the sports, and being able to show what they have
outside of school, basically.
Madonna believed that one of the motivations of the student is that they want to get better
themselves. Madonna shared that they also use incentives so that the student will be motivated
to get better. Madonna shared:
I think the motivation could be a reward system. Sometimes, we do behavior plans that
offer a reward that they want to work towards and learn. I think a lot of the times, it’s
also just in themselves – I want to be a better person, I want to do better, I want better
grades, I don’t want to get in trouble as much. I think a lot of that is internal.

87
RQ2: What do SBMHCs perceive as barriers meeting the mental health needs of
adolescents from a school district in Connecticut, United States?
The second research question was about the perceptions of the SBMHCs about barriers of
meeting the mental health needs of adolescents from a school district in Connecticut, United
States. To generate quality responses, I made sure that all the participants are active service
providers of SBMH or have a role in the process of students acquiring SBMH services. To
achieve this goal, I developed one interview question (IQ) and one follow-up question that were
answered by the participants:
Data analysis showed that all participant responses to these interview questions addressed
RQ2. All SBMHCs shared perceive barriers meeting the mental health needs of adolescents from
a school district in Connecticut, United States. Two themes emerged from the participant
responses to RQ2: (a) barriers that affected success of at-risk students and (b) factors that
influence lack of use of SBMH services by the students. Table 3 summarized the themes,
respond frequencies and subthemes that emerged from the participants responses.
Table 3
Emergent Themes, Response Frequencies and subthemes for Research Question 2
Research Question Themes Resp
Freq
Subthemes
RQ2: What do SBMHCs perceive as
barriers meeting the mental health
needs of adolescents from a school
district in Connecticut, United
States.?
Theme 3. Barriers that affect
success of at-risk students
Theme 4. Factors that affect
lack of use of SBMH services
24
20
21
18
10
Theme 3 Subtheme 1. Parental Involvement
and Engagement
Theme 3 Subtheme 2. School Attendance
Theme 3 Subtheme 3. Lack of resources (staff
and employees)
Theme 4 Subtheme 1. Stigma

88
8
Theme 4 Subtheme 2. Time Constraints
Theme 4 Subtheme 3. Lack of financial
resources

89
Theme 3. Barriers that affect success of at-risk students
The barriers that affect the success of at-risk students also revealed factors that serve as
barriers to meeting the mental health needs of the students. One-third of the participants
provided comprehensive answers to this interview question. Most of the participants have
identified two or all the subthemes mentioned. Most of the participants perceived that parents,
especially their family background or level of parents’ knowledge and understanding about
SBMH, were the greatest barriers to the success of at-risk students who need SBMH services.
Three subthemes emerged for this major theme: parents as a barrier, attendance of the students,
and lack of resources to address the needs of the students.
Parents as a barrier. Most of the participants mentioned parents as barriers to students’
use of SBMH services. The lack of parental involvement remains a crucial issue in the student's
mental health. There are programs students need to continue at home that is not done because of
parents.
Anna noted that the parents serve as barriers because they are not knowledgeable about
psychological and social disorders. Moreover, students are also limited in accessing SBMH
services because there are some programs that need parental permission or consent. Anna
believed that her school offer a wide range of SBMH services; however, they remain sometimes
unused because of this barrier. Anna stated:
I think a lot of the barriers are parents being uneducated about psychological and social
disorders. I believe that there are limitations for the students to access them without

90
parental permission. I believe that the services that we do provide, a lot of it is very
informative. And that kind of eats away at time that’s allocated for other tasks.
Debra explained that adolescents at risk often have multiple risk factors. She further
explained:
… so, we may be dealing with students who have mental health issues, but they also
have issues associated with poverty, and they have issues associated with housing
security and family security. So, with multiple issues, it’s really hard to disentangle and
figure out how best to help the students, because there is so many things for which they
need help. And oftentimes, these issues that they face impact attendance, so the kids who
maybe need our help the most are the ones that we don’t regularly see often enough to get
them the help they need.
Joy shared that in her two decades of being a counselor that the biggest barrier is the lack
of parental engagement. Julie also perceived that lack of parent support at home also serves as a
barrier. Julie stated:
And not having the support at home. That’s a big barrier, if the parents can’t be there, or
the guardians. Maybe their parents are in a different country. I have a lot of students
who have a new relationship with their parents because they were left in their country
with another relative. So, now they’re here with their mom that they haven’t seen in,
like, fourteen years. So that’s a barrier, because they have this big adjustment. It’s
outside of the regular transition to high school, which is already a big adjustment.

91
Madonna also mentioned that she has experiences of lack of parental involvement. She
commented that most of the time the parents are not on board with the programs or services that
their child need. Sometimes, it was even difficult to get a response from the parents. This is the
same struggle of Opera revealed that some parents do not even respond to her phone calls when
there is an issue with their child. Opera commented:
I’m really struggling with parental involvement. Oftentimes, the parents are also
experiencing the same problems that the children are: drug use, incarceration, termination of
parental rights, there are a lot of issues in the community. Economic issues as well; children
come to school without adequate clothing, so I provide that sometimes here for them. There are
children that have described to me that their home environment is – just a really poor place to
live. Rats overrunning their apartment. I have a child with asthma and I’m really concerned
about his constant symptoms, and it turns out that he has…you know, a rat infestation at home.
There’s children that sleep on different peoples’ couches at night and don’t go home at all. So,
those are some of the barriers that I’ve been encountering.
Wilbur shared the same sentiments with Opera. Wilbur commented that the background
of students should be taken into consideration. Wilbur added:
We have some students who come from very bad circumstances, yet they come to school
every day, they do their best to do their work, get their work done or whatever, and then
we have students who don’t come to school every day because of their circumstances,
and things of that nature. So, I think it’s that – the lack of support, you know, whether

92
it’s at home, or they don’t feel it at school; the lack of positive role models as well. I
think there’s a lot of things that impact how at-risk students operate.
Attendance of the students. The attendance of the students also influences their access
to SBMH services. Debra mentioned that students’ issues and problems at home affect their
attendance. This becomes a problem because the students who need their help the most are the
ones they do not regularly see at school. Joy also mentioned that student truancy is one of the
barriers of SBMH services as they cannot cater to students who are not present in school. Julie
highlighted the problem of truancy in the context of mental health:
So we have a lot of truant students; we have students who think it’s normal to – ‘oh, it’s
not that bad, I’ve only missed 20 days.’ {laughing} Uh, that’s not good! That’s like,
almost a month of school. So I think it’s a big issue, it’s not just mental health.
Lack of resources to address the needs of the students. SBMHCs perceived that there
is lack of resources to address the needs of students. Debra mentioned that students face
multiple risk factors and it takes a lot of time and effort to disentangle and figure out how best to
help the students. Most of the time they do not have the resources to address all the needs of the
students. Parents might also have resources as problem which is why the home setting of the
student is also problematic. Julie mentioned that the parents might have lack of resources. For
instance, the parents might have a job that do not let them have a typical schedule or they have
multiple jobs or shifts.
Maria and Sotomayor mentioned the lack of resources and the amount of workload they
have serve as barriers. Maria added:

93
So, personally, some of the barriers – and I’m speaking as a school counselor – would be
the caseloads that we have sometimes, and the workload sometimes does not allow me to
fully counsel students the way that I want to. Which is why we have all these other
services in the school that we refer to. I personally would like to do more counseling,
more group counseling with students if my time allowed. I would say that the workload
and the caseloads, unfortunately. In this school, especially, the resources are thinned, so
we are all left to do a lot of work. And sometimes, we have to hop in and do different –
you know, we have to wear different hats. Sometimes our roles and what we are really
meant to be here for, we don’t get to do that. We try our best, but that is a huge barrier.
Sotomayor has similar sentiments. Sotomayor added that there are only a small number
of professionals that are qualified to provide help to many students. Moreover, there is also a
high amount of work to be done. Sotomayor explained:
Here, we have the school psychologist, we have a social worker, we have a counselor,
and even with the three of use, we can’t keep up with the demand. And on top of – we
would like to focus on a lot of mental health problems, because you know, it is a big
problem and it does affect learning significantly, but there is also a lot of bureaucracy that
we have to deal with. I have a lot of deadlines for my testing, so that comes first. Which
is terrible, because you know, mental health issues pop up. You can’t put it on a
schedule, like ‘oh, I’ll do it with you next week.’ But sometimes that’s kind of what we
have to do. So that’s a huge barrier, I think. The need is too high and the professionals
who provide the help, there aren’t enough of us.

94
Theme 4. Lack of Use of SBMH services by students
SBMHCs shared their perceived barriers for lack of SBMH services use and meeting the
mental health needs of adolescents from a school district in Connecticut, United States. Most of
the participants provided answers to this question. Stigma was identified as the prominent reason
as students were still affected by how their peers perceive them and societal negative view of
mental illness. Three subthemes emerged for this five major theme: (a) stigma as a barrier, (b)
time constraints, and (c) lack of financial resources.
Stigma as a barrier. The majority, of the participants noted stigma as a reason for the
lack of use of SBMH services of the students. Students do not want to be labeled by their peers.
They will not use SBMH services if they think it will negatively influence how their peers
perceived them.
Barbara mentioned that stigma is a problem for mental health services. If students see a
student talking to a social worker or a school counselor, then they might make assumptions about
the life of the student. Barbara stated:
It could be the fear of what others may think. Their classmates. Some of them don’t
want to be seen speaking with, say, a social worker. So, some of them may not attend
sessions that they’re mandated to attend because of what other students would think.
That could be another factor. That also comes up as well. But, when you have other
students within the group assuring that one apprehensive student that this environment is
good; we have fun; we learn things. Most times, nine times out of ten, the apprehensive
student does come around.

95
Diva also answered stigma as the number one reason students do not use SBMH services
even if they need to. In some instances, the student would think they are fine and not use the
SBMH services, but their behavior would indicate otherwise. Diva further explained:
It’s – you know, I’m out in the street. They don’t need to know I’m on medication. I’m
fine, I can handle it all. And it’s unfortunate, because a lot of them, when they do go on
medication, you see the difference. We also know when they’re not on their medication,
they have such an off day. And we have parents coming in saying they don’t want to take
their meds; they pretend they take them, they spit them out. But I really think it’s, ‘what
are people going to think of me?’ Like, that stigma that I’m crazy or something’s really
wrong with me. And they don’t want to see themselves like that.
Joy stated that there is still the stigma that a person is crazy just because he or she needs
to talk to someone. There is a lack of knowledge and understanding for SBMH services. Julie
also provided stigma as a reason. Julie observed:
You know, they have this stigma. Some students. Most, I don’t think do. I think we do
have a lot of students that have a lot of need that do access all the school-based mental
health services. But some students might thing they don’t connect with that particular
provider; so either myself or my other colleague, or one of the other counselors, you have
to see what’s the best fit. Or their parents might not want them to, if they find out. So,
usually as a school, as a counselor, for brief intervention, I don’t call the parents and say,
hey, you know, I’m seeing your student for this. But, sometimes the parents find out
they’re seeing a social worker, or someone else, and they say they don’t want that to

96
happen. I think it’s all about the relationship. And also, time. I feel like I collaborate a
lot. So, when I’m meeting with social work interns who are working with my students,
they say ‘this student, I couldn’t get him out of this class because he was failing’ or ‘the
teacher wouldn’t agree to have them leave class.’ So, I think time is an issue. And not
interfering with academic work. And trying to figure out, what is the sweet spot in the
schedule, or seeing if the teacher will allow them to miss some class time and allow them
to make up the work later. So, I think that’s a factor of not accessing. And the stigma of
talking to the counselor or talking to a social worker. But I don’t feel like I’ve
encountered it that much. Yeah, those are the main factors, I would say.
Maria mentioned that the family background of the student might also be influencing the
stigma surrounding mental health services. Students may feel stigmatized if they seek a school-
based mental health service. Maria added:
Also, it has a lot to do with the way they grow up; certain cultures, certain families, feel
that ‘we don’t bring our problems to other people, we don’t discuss, we keep this in our
circle.’ Students are probably more hesitant to seek that help. That’s what I see.
Sotomayor also perceived stigma as a reason for the lack of use of SBMH services. The
wrong assumptions that caused stigma must be clarified. Sotomayor further discussed:
A lot of the time, people think ‘oh, you’re going to see a psychologist, or a counselor,
there’s something wrong with you!’ So, I think that’s definitely something that we need
to continue to work on to normalize.

97
Time constraints. Time constraints were also identified as a reason for the lack of use of
SBMH services by the students. Anna mentioned that time is a reason for the lack of use because
of wrong assumptions about psychology that are still prevalent today. Julie discussed that using
SBMH services might mean interfering with the students’ academic work. Julie explained:
So, I think time is an issue. And not interfering with academic work. And trying to
figure out, what is the sweet spot in the schedule, or seeing if the teacher will allow them
to miss some class time and allow them to make up the work later. So, I think that’s a
factor of not accessing. And the stigma of talking to the counselor or talking to a social
worker. But I don’t feel like I’ve encountered it that much. Yeah, those are the main
factors, I would say.
Lack of financial resources. Anna, Maya, and Sotomayor mentioned that financial
resources and the lack of it was one reason that students do not use SBMH services. Maya
mentioned that there are other factors that needs to be addressed and sometimes the SBMH
personnel cannot address these factors. Maya added that monetary aspect is also an issue for the
parents and the students. Wilbur also asserted that money was an issue. Wilbur discussed:
If money was not an issue, I’m sure we would have a ton of resources. But, at the end of
the day, all these resources cost money, whether it’s salary, programs, space. And I think
that’s the biggest hindrance to creating more programs to deal with more kids. And you
see that, I think, through society. When you think about, in prison, how many of those
prisoners have real, severe mental health issues and are not really being dealt with. And
then you see them at the school level, and the lack of some of those resources impacts

98
how students do. And I think that’s a bigger – I don’t think that’s just a school issue; I
think that’s a bigger societal issue that we don’t necessarily deal with. Okay?
Summary
The purpose of this study was to examine SBMHCs perceptions about factors affecting
the use of SBMH services by adolescents ages 12 to 17, from a school district in Connecticut,
United States. The objective of this chapter was to present an analysis of the lived experiences
of SBMHCs. To gain a deeper understanding about the phenomenon of using SBMH services.
Two research questions guided this study. Fifteen participants agreed to participate to the study.
The 15 participants provided responses that were transcribed and analyzed to present the analysis
in this chapter. There were five themes that emerged from the data analysis: (a) recipient of
SBMH services, (b) identification of students who use SBMH services, (c) motivations of
students to use SBMH services, (d) barriers that affect success of at-risk students, and (e) factors
that affect lack of use of SBMH services. In Table 4, the themes, subthemes, and key findings
are outlined. In Chapter 5, the discussion, interpretation, and implications of the findings was
presented.
Table 4
Summary of the Results
Themes Subthemes Key Findings
Theme 1. Identification of students who use
SBMH services
Theme 2. Motivations of students to use
SBMH services
Theme 1 Subtheme 1. Referral system (self-
referral, teacher referral, parent referral, staff
referral)
Theme 1 Subtheme 2. Academic data
(grades and attendance)
Theme 2 Subtheme 1. Established a trusting
relationship (rapport)
•
Well-established and trusting
relationships motivate students to
use SBMH services.
• Trust is an important concept in
using SBMH services

99
Theme 3. Barriers that affect success of at-
risk students
Theme 4. Factors that affect lack of use of
SBMH services
Theme 2 Subtheme 2. Incentives
Theme 3 Subtheme 1. Parental Involvement
and Engagement
Theme 3 Subtheme 2. School Attendance
Theme 3 Subtheme 3. Lack of resources
(staff and employees)
Theme 4 Subtheme 1. Stigma
Theme 4 Subtheme 2. Time Constraints
Theme 4 Subtheme 3. Lack of financial
resources
• Parents served as a major barrier
in the students’ use of SBMH
services.
• Students who have perfect
attendance were more likely to
receive and use SBMH services
compared to students with poor
attendance
• Stigma is one of the major
barriers why students will not use
SMBH services.

100
Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
Education in the United States requires a joint coalition of principals, teachers, parents;
school-based health service providers, counselors, and others in the school counseling; the
government; and the community at large. Any number of reasons can alter a student’s academic
outcome and social wellbeing. The students’ academic outcomes and behavior can be related to
broader systematic factors such as familial health, culture, demographics, economic status, and
mental health (Craun, Haight, DeCou, Babbitt, & Wong, 2017). Emotional wellbeing and mental
health have an impact on learning and development (Cuellar, 2015). The adolescent’s mental
health is related to interpersonal relationships, social skills, academic motivation, disabilities,
crisis prevention, school safety, and substance abuse. A student’s mental health can be
compounded if a student is experiencing risk factors.
SBMHCs’ perceptions were relevant for
this study because they are better positioned to address the unmet mental health needs and life
trajectories of all adolescents including those experiencing family relationship issues, negative
community influences that impacts their ability to excel academically, or lack of resources to
improve their life paths for the future.
SBMHS are designated to provide services to address and improve the unmet mental
health needs of all students to enhance academic achievements. SBMHCs work in tandem with
psychologists, nurses, social workers, teachers, and others in the school counseling settings.
School-based counselors are on the front line to help these students with mental health needs. As
Collins (2014) pointed out, the perspectives of SBMHCs are often left out of scholarly studies

101
that focus on aiding adolescents with mental health issues. SBMHCs’ role and work with
adolescents in the school settings has evolved for over 100 years and has been mired with
professional identity constructs, such as outdated services models and persistent problem with
use and supervision of SBMHCs (Cinotti, 2014). There was a gap in research on examining
SBMHCs’ perceptions on why significant number of adolescents are not using SBMH service
and how to improve SBMH services based on their insights. A collaborative effort between
schools, families, and SBMH professionals could positively augment adolescents’ academic
achievement and mental wellbeing (Lewis et al., 2015).
The purpose of this descriptive, phenomenological approach was to examine the
perceptions of SBMHCs about factors affecting the use of SBMH services by adolescents from a
school district in Connecticut. Face-to-face, semistructured interviews of 15 SBMHCs was the
primary method of data collection. NVivo software helped organize data and isolate pertinent
themes. The results of SBMHCs study could contribute to the literature on school-based
counselors and build broader consensus on the unmet need of mental health service use by
adolescents. According to Algozzine, (2017), SBMH administrators need assistance with
identifying and supporting SBMHCs implementing effective interventions for all adolescents. It
is important that a more significant focus be placed on SBMHCs to help alleviate this
phenomenon.
In this inquiry, a qualitative, phenomenological approach was used to improve the
understanding and elucidation of SBMH services and the perspectives of professionals in the
field. Qualitative research was the best approach for the study as it permitted the use of

102
techniques that focused on the details of how and why of the phenomenon (Kelly et al., 2015;
Yilmaz, 2013). Through a descriptive, qualitative account of the SBMHCs’ position and feelings,
an in-depth investigation yielded pertinent topics on how and why adolescents use SBMH
services.
A phenomenological approach was appropriate for this research as it aided in the
understanding of the shared perceptions of SBMHCs. Phenomenological researchers gather
individual accounts of the phenomenon to create a better understanding of the topic.
Additionally, phenomenology aligned with the chosen instrumentation to gather data: primarily
interviews. Sutherland and Cameron (2015) stated that interviews document, enhance, and enrich
insights, clues, and rapport with the participants. Interviews also allowed the interpretation of
the data and facilitated replication of the research process for further studies. Additionally,
interviews permitted improved flexibility with the use of follow-up questions and observed data,
which focused on the participants’ variation of essential themes that were then highlighted.
SBMHCs collaborate with other professionals such as psychologists, teachers, social
workers, nurses, or others in the school counseling settings and community agencies. SBMHCs
and these other professionals are often the first responders when identifying students with mental
health needs. SBMHCs must be acquainted with a variety of tools to assess a student’s mental
health and create prevention and intervention plans while making referrals for further treatment.
All these decisions revolve around a student’s mental health, ability to perform academically,
and behavioral problems (ASCA, 2015).

103
SBMHCs often spend up to 1,700 hours in training, in addition to academic qualifications
before they can communicate with adolescents regarding their mental health need (ASCA, 2015).
These requirements are necessary as schools are meant to provide students with the ability to
develop knowledge and social skills necessary for their future. Despite the requirements,
SBMHCs’ opinions are rarely incorporated when developing new policies for mental health care
(Collins, 2014). SBMHCs, instructors, and parents are responsible for protecting students’
positive mental health and improving academic outcomes. The promise of improving SBMH
services necessitates a change from focusing on behaviors of adolescents to actively sharing
responsibilities with SBMHCs. Any action to preventing, reducing, and encouraging students to
use SBMHs, and/or intervening in school-based problems should not be the responsibility of any
one group or individual (Algozzine, 2017). SBMHCs, others in the school counseling,
adolescents, and parents all need assistance; communities need help supporting the schools.
SBMH services have been under researched, and previous researchers focused on measuring the
effectiveness of SBMH services rather the perspectives of the involved professionals, (Williams
et al., 2015; Wrigley, 2015). Similarly, Adams (2015) suggested that new research is needed as
current studies did not include SBMHCs’ perceptions, thereby limiting recommendations to
improve SBMH services and reduce discrepancies and difficulties within the system.
Understanding SBMH professionals’ perceptions could contribute to new strategies for building
relationships with students that could help alleviate the unmet mental health needs of
adolescents.

104
SBMHCs’ perceptions could also support school administrators’ decisions when
implementing and amending programs meant to bolster student outcomes and mental health.
These perceptions may offer clarity on how to improve outreach to new students and
participation of students already within those programs. Whether it is economic, cultural, or
behavioral issues, it is vital to understand the differences between programs and why students are
not using these services. The results from this study could improve administrative protocols and
provide new policy options for an increasingly diverse student population. These perceptions
might identify the difficulties of where collaborations between SBMH facilitators and the
participants and support staff are failing.
Two research questions were asked to understand SBMHCs’ perceptions about students
use of SBMH services. The first research question was the following: What do SBMHCs
perceive as factors that may affect the use of SBMH services by adolescents from a school
district in Connecticut of the United States? The second research question was the following:
What do SBMHCs perceive as barriers meeting the mental health needs of adolescents from a
school district Connecticut United States? From these two research questions four themes were
uncovered: (a) identification of students who use SBMH services, (b) motivations of students to
use SBMH services, (c) barriers that affect success of at-risk students, and (d) factors that affect
lack of use of SBMH services.
This chapter will begin by interpreting these themes in terms of the literature and
theoretical framework. I revisit the limitations of the study, offer practical recommendations for
future research, and examine any implications. These implications could relate to positive social

105
change as well as recommendations for methodological, theoretical, and empirical implications.
The implications will also include recommendations for practical solutions identified by the
participants. This section will end with a conclusion summarizing the chapter as well as the study
itself.
Interpretation of the Findings
Research Question 1
Research question one asked two questions, and one follow up question to identify any
prevalent themes and related sub-themes. These questions were ‘based on your experience, who
most often receives school-based mental health service and why? ‘In your opinion, what do you
think motivates adolescents to utilize these services’, and ‘do you have a specific way of
identifying these adolescents in need?’ The last question was used as a follow up to question
two. From these questions three themes were developed: recipient of SBMH services,
identification of students who use SBMH services, and motivations to use SBMH services. Five
sub-themes were established: Identification of students who use SBMH services, referral system,
academic data such as grades and attendance, establishing a trusting relationship, and incentives.
These sub-themes will be discussed when relevant to the literature.
Theme 1: Identification of Students Who Use SBMH Services
To better improve SBMH services and counseling, it is vital for SBMHCs to identify
students who need help the most. Collaboration between different members of the school and
improved referral systems are necessary for increased participation in SBMH services. The
findings for the identification of students in need for SBMH services were consistent with

106
majority of the study participants responses, confirmed that implementing a collaborative process
in schools can help improve the identification of adolescents who may need care the most.
Changing the lens of how adolescents who needs help are identified and using tier-support offer
opportunity to reduce bias making judgments and decisions that focus on behaviors of students,
(Algozzine, 2017)
Paternite and Johnston (2005) examined the variables within a school’s environment
which can aid or limit a student’s need to reach out for help. One problem uncovered was that
there is often a strained relationship between teachers and mental health professionals. To
ameliorate this difficulty, the authors suggested improved dialogue and collaboration between
the parties, thereby creating better outreach to students. Eklund, Meyer, Way, and Mclean
(2017) also suggested that collaboration is needed between teachers and school psychologists to
better serve the students. Similarly, Brun et al. (2016) suggested that there should be purposeful
collaboration among teachers and mental health professionals to address the needs of the
students. This suggestion supports a consensus solution proposed by SBMHCs to address unmet
mental health needs of all students.
The literature noted that collaboration for identifying troubled students goes beyond just
the school itself. School psychologists must combine their efforts with parents and school
professionals to increase mental health screening and recommendations for increased counseling
(Splett et al., 2013). This is supported by the participant answers as they stated that their diverse
group and support system greatly helped in giving students an opportunity for the use of SBMH
services. Many scholars have stated that by expanding the role of school psychologists, SBMH

107
services and outreach can be improved (Eklund et al., 2013; Graves, Proctor, & Aston, 2014;
Splett et al., 2013). Lastly, Lynn et al. (2003) detailed that a strong relationship between social
workers and SBMH professionals can help at-risk students increase their academic performance.
A strong collaborative system is important; however, it is equally urgent that students do not slip
through the administrative cracks. Therefore, a referral system is needed.
Different Referral Systems. The Participants stated a variety of referral systems to
identify students who use SBMH services. Some of the participants’ schools used a holistic or
team approach for referral allowing any student, teacher, staff, parent, or an external agency to
recommend a student for SBMH counseling. Alicia pointed out her school’s SSST system which
offers recommendation for appropriate services to the student. Should this service not be a
proper fit, the students are moved into a different program until their needs are adequately
addressed. Maria’s school employs child study meetings to identify and refer students to SBMH
programs. Maya stressed the importance of teams to help refer students. However, Anna and
Sophia found that teachers were the prime facilitators when referring a student to counseling as
they could best identify bad behavior or poor academic achievement.
These statements from the contributors are supported by Wegmann et al. (2013) and
Bear, Finer, Guo, and Lau (2014) who found that collaboration among caregivers, family,
professionals, and teachers are needed to address a student’s mental health. Splett et al. (2013)
detailed that mental-health intervention procedures need to be updated. School psychologists are
in a unique position to aid students and amend mental health practices at their school (Splett et
al., 2013). Cohen (2016) asserted that a school nurse should not be left out of the referral system

108
as they attend to a student’s psychological and emotional needs, often making them one of the
first responders. Ramos et al. (2013) found that nurses had responded to adolescents’ mental
health emergencies, and were involved with cases of child abuse, neglect, depression, and
violence at school. By including these two positions in any referral system SMBH outreach and
services could be greatly enriched. Despite identifying key features of a referral program, it is
important to understand what motivates a student to use SBMH services.
Theme 2: Motivations of Students to Use SBMH Services
The third theme, motivations of students to seek out SBMH counseling, described that
trust was an important issue for students when considering help. Student-professional
relationships were imperative to be maintained for students to seek help. Two sub-themes were
identified in this section: established and trusting relationships and an incentive program.
Established and Trusting Relationships. The majority of the participants detailed that
students who do utilize SMBH services do so because they feel safe and trust the professional
involved. The trust permits students to find adults who may sympathize and offer support or
help for the plight of the student. Should this trust be broken, students would remain reluctant to
use further the services most participants stated. Joy stressed the importance of a trusted
relationship, stating that she makes it a point to create an open and honest rapport with her
students. She adds that by having an SBMH team, students have greater access to professionals.
Joy also mentioned that parental involvement is important. Anna echoes these sentiments
by declaring the only time she breaks the trust is when a student’s action goes against the law.
Debra specified that teachers should go out of their way to establish trust with the students while

109
Julie and Opera found that students’ approach those whom they feel that can be trusted.
Therefore, Julie stresses that being accessible to the students is vital. Maria detailed that this
trust begins with school culture, where engagement is encouraged, creating a need for a more
unified and supportive learning environment. Although, not directly correlated, Gamble and
Lambros (2014) stated that staff development and better decision-making is imperative to
establishing trust. whilst, Bains (2014) found that students tend to seek out the opinions of their
classmates before seeking help from an adult. These findings provided the biggest discrepancy
between the participants’ statements and the literature. At no point was student support or
assistance from other students specifically discussed. While, school culture may facilitate a
student body more open to seeking help, other students’ perceptions must be analyzed, especially
when students feel that asking for help may be stigmatized by their classmates.
Incentives. The Participants also established a sub-theme of incentives. Incentives could
help encourage students to seek out help from SMBH officials. Alicia employs positive words
and offers prizes to students to help connect with the teachers. Diva said her school uses sports
as an incentive for students to maintain scholastic achievement and rapport between student and
teachers. Technology, gold cards, and white sheets were also mentioned as incentives. Madonna
felt that perhaps the best motivator came from the student themselves. While incentives may be
beneficial for some adolescents, students must be open to change for any program to work.
Incentives were not covered in the literature review in Chapter 2 creating a need for future
research on how incentives fit in with existing scholarly research.

110
Research Question 2
This research question sought to assess the perceptions of SBMHCs about the barriers
preventing adolescents within a school districts in Connecticut, United States from seeking
mental health services. To examine this research question one interview question was developed
along with one follow up question. The interview question was ‘what barriers do you perceive
affect best outcomes for adolescents at risk?’ The follow-up question was ‘please describe the
factors you attribute to lack of use of school based mental health services used by some
adolescents.’ From the responses to these questions two themes emerged along with six sub-
themes. The main themes were barriers that affect the success of at-risk students and the factors
that affect lack of use of SBMH services. The sub-themes were parental involvement and
engagement, school attendance, lack of resources, stigma, time constraints, and lack of financial
resources.
Theme 3: Barriers that Affect the Success of At-risk Students
The first theme addressed barriers that may prevent at-risk students from seeking mental
help from SBMH services. To understand this theme, the sub-themes of parental involvement
and engagement, school attendance, and lack of resources were developed. Roughly one-third of
the participants provided in-depth answers to this interview question and most agreed with two
or more of the sub-themes. All the participants (100%) acknowledged that family background,
parental knowledge and support were the main causes of adolescents not seeking SBMH
services. The other two themes, while significant, were less agreed upon.

111
Parental Involvement and Engagement. Parental involvement remains an essential
construct of at-risk students seeking help. Should the student seek SBMH counseling, parents
have an additional responsibility to follow-up on the programs at home. Anna stated that many
parents just do not recognize psychological and social disorders. Additionally, having to receive
mandatory parental consent before beginning some of the programs can also be a deterrent. Joy
and Julie also supported the opinion that parental involvement is the biggest barrier in seeking
help. Madonna elaborated upon this sentiment by stating that parents are often not on board with
the offered programs, while Opera opined that it is often difficult to get parents on the phone to
discuss what the SBMH program is and how it would be beneficial. Wilbur affirmed this
statement while pointing out that when dealing with parents, the socioeconomic and cultural
backgrounds must be considered before engaging.
Ling et al. (2014) supported Wilbur’s assertion. Ling et al. examined the unmet mental
health care needs of Asian American adolescents within urban communities and concluded that
family dynamics such as structural stressors, social stigma, and discrimination can all influence
whether these students receive help with their academic and emotional difficulties. Parental
influence is just one barrier, another major complication is attendance. Moreover, Bear et al.
(2014) also noted that family characteristics such as racial background and socioeconomic status
should be evaluated to determine the most appropriate approach in helping students.
School Attendance. School attendance is another element in why students do not
receive mental health counseling from SMBH services. Debra, Joy, and Julie were the main
participants who spoke emphatically on the issue. Debra began by maintaining that problems at

112
home can affect student attendance. Those who have problems at home, often have difficulties
preventing them from seeking help despite being those who need counseling the most. Debra
also commented that this can be a vicious cycle as continued absence prevent needed counseling.
A poor family structure can decrease attendance and exasperate mental health problems.
Problematic absenteeism among 14 % of the United States student population is a national
concern that can have negative consequences on adolescents’ emotional, social, academic
functioning and their psychological wellbeing (Craun et al., 2017). Yet by not going to school to
receive treatment, these problems can grow to negatively affect adolescents’ academic outcomes
and lives at home, thereby worsening the problems for everyone involved. Joy and Julie both
noted that students who are often truant are unable to get the help they need resulting in more
truancy. This theme was confirmed in a recent literature creating a need for future research and a
focus on attendance within the context of SBMHCs’ perceptions on this issue.
Lack of Resources. SBMHCs stated that a lack of resources prevents them from
reaching the number of students who need help. Debra pointed out that many resources are
needed to understand the interweaving issues regarding mental health help, while Julie stated that
resources must be present at home as well at school, adding that parents often lack the time or
money to adequately provide what is needed for their kids. Maria and Sotomayor pointed out
that the amount of time they need versus the resources provided do not make it easy to tackle the
number of students in need of care. Sotomayor and Wilbur determined that qualified counselors
and finance are also a limited resource.

113
Suldo et al. (2010), in a study focusing on factors that create barriers to SBMHCs, found
that school environment, poor training, and a lack of support from administrators to provide them
with the resources needed are prime causes of poor SBMH availability. The authors advocated
that SMBH counselors must be involved in administrative budgeting to ensure quality care.
Gamble and Lambros (2014) study supported this assessment stating that inadequate resources
and access to services are detrimental to SE schools within the northeast United States. These
findings line up with the United States. Census Bureau (2014) statistics, which found that 37.6%
students live below the poverty line, making it difficult for schools to offer the resources needed
to address adolescent mental health needs. Wang, Do, Frese, and Zheng (2018) found that lack
of resources of the school to have culturally responsive interventions was a barrier to immigrant
students’ access to SBMH services.
Theme 4: Factors that Affect Lack of Use of SBMH Services
The responses from the participants also uncovered three factors that can contribute to
why students do not pursue SBMH services and counseling. The overwhelming response from
the participants (100%) was that, the stigmatization that students may receive from peers and
their own family. Other themes found were time constraints and a lack of financial resources.
Kidger et al. (2009) studied 296 English secondary schools and found that support for SBMH
services varied greatly. Students responded that confidentiality is necessary for student
participation. The authors also uncovered a need for a supportive school environment to
encourage adolescents to use SBMH services. Participant responses coupled with the literature

114
indicated a need for teachers and administrators must provide a confidential and supportive
environment for SBMH to thrive.
Stigma. Social stigma was found to be a major issue in why students do not seek SBMH
services. This is because students do not want to be categorized by their peers in a negative
light. Diva mentioned that this stigma prevents students from getting help even though their
behavior demonstrates a need for it. Joy felt that by merely admitting that a student needs
someone to talk adolescents may be branded as being “crazy”. Maria brought up that a student’s
home life or culture may influence their decision to seek help as some families may stigmatize
mental health.
The literature expands upon these concerns. Eklund et al.’s (2017) study acknowledged
that there is still stigma when it comes to students seeking help for their mental health issues.
Wu et al. (2010) found that there is a poor concept of what mental health entails, as well as
uncovering that ethnicity can cause students to ignore SBMH services. Bentancourt et al. (2015)
stressed that negative perceptions of mental illness and mental health affects those with mental
illness into refusing treatment. While their study focused on Somali Bantu and Bhuatanses
refugee adolescents, the findings, supported the notion that culture, or ethnicity may contribute to
the refusal of help. The authors called for culturally sensitive programs to counter the stigma.
Bogart et al. (2013) found that African American and Hispanic students had more stigmatization
of mental health than other races, confirming both findings in the literature and assertions and
inferences of SBMHCs ( 95%) shared experiences in this study.

115
Time Constraints. Another uncovered sub-theme was time constraints. Time constraints
for both students and SBMHCs can limit the amount of services and options to students. Julie
asserted that SBMH services can interfere with a student’s academic life. Anna was concerned
that poor assumptions of what mental health services are coupled with limited time can influence
a student’s lack of interest in SBMH treatment. Since, there was no relevant literature within
Chapter 2 that directly pertained to time constraints. Recent research confirmed that time
constraints predicted emotional exhaustion for SBMHCs, and positive school atmosphere has
potential to facilitate optimal school setting needed to support, student learning and growth,
parents’ experiences; inclusive educational practices and the wellbeing of SBMHCs, (Gray,
Wilcox, & Nordstokke,2017), As this was a sub-theme, future in-depth research may be needed.
Whilst time can be considered a resource, five participants indicated that a lack of financial
resources can also prevent students from receiving SBMH services.
Lack of Financial Resources. A lack of financial resources was also found to be a
significant sub-theme as funds for SBMH professionals and programs may greatly improve their
effectiveness. Anna, Maya, and Sotomayor attributed poor financial resources as a major reason
why students do not seek assistance. Maya expanded upon this elucidation by mentioning that a
lack of monetary funding restricts professionals from addressing many of the concerns that go
beyond mere school counseling.
Despite SBMH services being available to students, the capacity to reach adolescents is
still limited by funds, thereby barring quality treatment to many students (Wu et al, 2010). Lack
of funding may be a result of variation of SBMH services that are often not clearly defined

116
(SAMHSA, 2015). Funds for SBMH can come from the Special Education Act or IDEA as well
as the State Children Health Insurance Programs. However, restrictions imposed by these
funding sources can diminish the types and duration of those services (Gamble & Lambros,
2014; SAMHSA, 2015).
Theoretical Framework
The theoretical framework employed in this study was Mechanic’s (1979) theory of help
seeking. This theory has ten constructs: stages of illness, assessment of symptoms, impact on
other aspects of life, frequency, capacity to endure, available information, culture, perceptual
needs, the priority of needs, interpretation of symptoms, and resource availability for
understanding determinants of help-seeking and service use. While Mechanic’s theory offers a
broad perspective for understanding how adolescents seek help, it does not necessarily
correspond to the uncovered themes. The help-seeking model was not entirely irrelevant as it
focused on specific paradigms of an individual’s attitude in seeking mental health, such as the
pros and cons and the pressure of using SBMH services (Lindsey et al., 2013).
When assessing the model in the context of the uncovered themes, it is important to
compare the ten constructs with the study’s findings. Stages of illness were not directly
addressed within the uncovered themes. While, it is comparable to barriers to SBMH that affects
at-risk students the focus of this study was about SBMHCs perceptions. Should a student be
unaware of the level of illness, they would be less inclined to seek help. In that manner, the
stages of illness could be considered a barrier.

117
Assessment of symptoms was also not discussed directly. Some participants noted that
poor attendance or bad behavior could be indications of poor mental health. Should SBMHCs
catch that early, it may lead to a better evaluation of mental illness. Impact on other aspects of
life could also pertain to attendance and student outcomes. Not seeking SBMH services could
influence a student’s personal and academic life. The interpretation of symptoms was not
addressed and was difficult to form a direct correlation to the uncovered themes. Though,
attendance and student behavior could relate to the interpretation of symptoms. The impact of
other aspects of life also corresponds to teachers being able to identify those who need SBMH
counseling.
Frequency, the capacity to endure, and available information do not have correlation to
the stated themes, making comparison difficult. Culture was largely discussed, both in terms of
ethnicity, home structure, and academic environment. The Participants agreed that all three of
these factors can determine if a student seeks mental health help. While the priority of needs did
not come up with the themes, interpretation of systems did. It is up to SBMHCs to assess a
student’s mental health for proper referral to the matching programs and treatment. Resource
availability was an established theme found among the answers. Resources are a major part of
aiding students in seeking SBMH services.
Out of the ten constructs, only two were directly referenced to the found themes: culture
and resource availability. While some constructs did not relate at all, many others worked in
tandem with mental health assessment and referral. Whether it be behavior or attendance, it
seems that education professionals and SBMHCs have a large responsibility to understand the

118
stages of illness, assessment of symptoms, impact on other aspects of life, and interpretation of
symptoms. Further work is needed to understand the discrepancy between these findings and
why the remaining eight elements were indirectly addressed or not addressed at all.
Limitations
In qualitative studies, subjectivity is a concern for researchers and readers of research
outcomes. Subjectivity can influence the outcome of the study. Ratner (1997) stated that
subjectivity can contradict objectivity as a researcher makes decisions through a personal lens
during the investigation. Shelton et al. (2014) suggested that researchers should understand their
personal values and objectives to assess how they might have influenced the conclusions. In my
research, subjectivity was the main limitation because of my presence and the inherent
challenges for a novice researcher conducting interviews with study participants. Additionally,
some participants might have been apprehensive or cautious to answer the questions openly and
honestly, furthering the chance of misinterpreting the results. I minimized the limitations of this
study by implementing strategies that included: a) conducted a pilot study to ensure that research
instruments worked as intended to capture the lived experiences of SBMHCs. b) Used a
semistructured interviews open ended, c) I developed interview protocol used with SBMHCs
from a similar study (Gamble, & Lambros, 2014) d) Engaged in active thinking of reflexivity,
which enabled me to re-examine any assumptions and preconceived notions of the study. By
constantly assessing the researcher’s knowledge, attitude, and pre-existing thoughts, reflexivity
limited the personal perspective of the investigator, producing more objective deductions
(Chan,2013). In this study, adequate measures were taken to minimize bias, including the use of

119
a professional data transcriber, NVivo software, audit trail of my decisions, and maintaining
member check with frequent contact with committee chair to discuss, review the research
process and for guidance as needed.
Recommendations
Upon reviewing the results of this study, recommendations can be broken down into two
separate categories: research and methodology. The first step for further research should be to
examine where the results do not directly correspond to the literature review. Although sparse,
there were themes that were not prevalent when comparing the themes to the literature. Topics
that were discovered in the study, but not covered in the literature review were school attendance
and time constraints.
School attendance was cited numerous times across a variety of themes. It could be used
to identify students who need help as well. It also corresponds to scholastic success. There is no
doubt that attendance does affect students, therefor it should be furthered studied why it was not
prevalent within Chapter 2. Future research regarding attendance should focus on how SBMHCs
could aid in reducing truancy as well as any other corresponding factors between SBMH and
attendance that has not already been discussed.
Time constraints were mentioned in the themes, but not in the literature review. The
closest theme that comes close to covering time constraints, is the lack of available resources, as
time is often viewed as a resource. Time constraints was confirmed by recent literatures. Time
constraints predicted emotional fatigue for SBMHCs, and positive school atmosphere has
potential to facilitate optimal school setting needed to support, student learning and growth,

120
parents’ experiences; inclusive educational practices and the wellbeing of SBMHCs (Gray,
Wilcox, & Nordstokke, 2017). To fill this gap in research, further study is needed as to where
and how time constraints limit SBMHCs effectiveness. Bains (2014) stated that students seek
support and advice from students before seeking help from SBMHCs. While, Bain’s (2014)
assertion could align with the sub-theme of stigma, as students care about what other students
think, it was not specifically discussed by the participants causing a need for further expansion.
Further research is also needed to understand how and where the theoretical framework
differs between the outcomes. As I have previously discussed there were constructs of the
theoretical framework which did not connect to the discoveries of the study. Although this study
was about SBMHCs perceptions about factors and barrier that affect adolescents use of SBMH
services and was not focused on collecting medical information of the students they serve.
These constructs were stages of illness, assessment of symptoms, frequency; capacity to endure,
available information, and priority of needs. While some of these factors could be tailor-fitted
into the established themes, further investigation is needed to examine why these factors did not
directly relate to the results. Future research should frame interview questions around these
theoretical factors to further the applicability of the framework to the subject and find if these
new revelations could be used to identify more themes to create greater awareness of the
importance of improving SBMH services for better health outcome for adolescents.
Further research could also benefit from the measures taken or strategies implemented in
this study to minimize bias or place additional emphasis on reflectivity. Reflexivity is an
important concept in qualitative research that aims to prevent issues of trustworthiness in

121
qualitative research findings. Reflexivity helps to evaluate the actions or unintended prejudices
emanating from social relations between the researcher and the study participants referred to as
“asymmetrical power relations” by Kavel (2002). By adding multiple safeguards against bias,
the study’s findings could be further validated. Additionally, any other study looking to expand
upon this investigation would have greater transferability as the study would be better protected
against any bias. Last, this study can be expanded in any number of ways. For instance, this
study should be replicated in a variety of geographic locations with other school districts to see
where the differences lie. The consensus of SBMHCs context among the identified themes
supports that study results could lead to even better administrative decisions. Quantitative
research could also be applied to see how resources, student outcomes, and SBMH counseling
statistically influence each other. These findings could either corroborate this study or create
questions about where the conclusions differ, creating the need for even further research. Many
of the deductions drawn in this study can already provide implications for practice.
Implications
There are a variety of practical and academic implications of this research. This study
could support the need for future funding and greater resources. Both the literature review and
all the participants (100 %) stated that funding is a major issue in having adolescents receive the
help they deserve. However, as this study states, the call for resources might not always be heard
as SBMHCs are often left out of administrative decision making. At the very least, the results of
this study demonstrated a need for SBMHCs to be more involved on the administrative side to
ensure better student outcomes.

122
Another practical application is that there needs to be greater awareness among students,
the staff, and administrators of the importance of SBMH counseling. Whether it is SBMHCs
being better trained in building better relationship and identifying vulnerable students or
instructing learners to be more aware of their own emotions or changing the lens of how students
in need are identified, and increased awareness of mental health solutions is imperative.
(Algozzine, 2017). Greater awareness corresponds with better outreach to the students. Students
must feel comfortable with the SBMHCs and their teachers to seek advice and help. Though,
some students may feel disinclined to reach out if they do not have a personal relationship with
SBMHCs. Therefore, much of the burden falls on the SBMHCs to establish these connections.
Instructors and administrators must be better trained in the identification of problem behavior
and emotional challenges. Teachers should also be instructed in how to foster better
relationships with their pupils. This training could make the referral process more streamlined
and accurate.
Training should not stop at student identification. The results of this study, confirmed by
the literature review, indicated that instructors and SBMH professionals must be well-versed to
deal with the student’s family life and cultural traditions. By understanding how a culture or
family life could influence a student’s perception of seeking help for mental and emotional
issues, SBMHCs outreach could be improved. It would also help form relationships with the
parents, which the results also confirmed is a vital piece of SBMH treatment. Parents must be
prepared in the challenges their child may face as well as steps that can be taken at home.

123
Increased awareness of cultural aspects could aid teachers in better framing their conversation
about mental health.
As I mentioned in my recommendations, there are numerous ways to further progress this
research, both in terms of methodology and theoretical framework. The theoretical framework
did not entirely relate to the study. These discrepancies should be noted to see if the results can
be transferred in future studies. The methodological implications indicated that while this study
provided perceptions by SBMHCs in a specific geographic location, the conclusions may not be
entirely transferable. Additionally, there were no quantifiable data to compare how these
assertions relate to student outcomes. This study may be moot if SBMH counseling does not
correspond to student outcomes. Therefore, there is a need for further quantitative research.

124
Conclusion
In this study, I examined two research questions to extrapolate and expand upon the
perceptions of SBMHCs on student participation for mental health services. A comprehensive
literature review provided context to these research questions and the theoretical framework. The
methodology used was suitable for generating multiple themes and sub-themes. The uncovered
themes largely detailed the identification of those who need SBMH services and the barriers
preventing students from seeking those services. The participant’s responses supported each
other, with no real dissention or contradictions between statements, rather expansions upon other
participants’ responses. Yet the literature did not completely support all the statements.
Although, that does not suggest that previous research counters participant assertions; instead
they were not addressed in the literature review causing a need for reexamination of prior
research in the context of the results. While this study focused on a specific geographic area, it
would be beneficial for future research to examine other locations to see if these findings true
among various demographics. Additionally, quantitative work can be performed to determine
how these themes compare to student outcomes. In conclusion, SBMH services are faced with
variety of challenges that negatively affects adolescents’ access and motivation to use services. It
is was important to get information from SBMHCs to explain the challenges and possible
solutions based on the experiences.
Findings from this study, will hopefully raise awareness of
the importance of identifying students who may need SBMH services, improve trusting
relationship between SBMHCs and students, increase parental involvement, reduce students fear
of stigma to improve their motivation to use services.

