


1
CHAPTER 1
INTRODUCTION, BACKGROUND AND SIGNIFICANCE
Introduction
In March 2019, a novel disease began sweeping through nearly every country in
the world. Coronavirus disease 2019 (COVID-19) caused massive death and debilitation
and successfully changed the daily routines of many societies. The World Health
Organization (WHO) began response to the COVID-19 outbreak in China at the
beginning of January 2020. As the spread continued, the WHO declared a Public Health
Emergency of International Concern (PHEIC) on January 30, 2020 and ultimately
declared a pandemic on March 11, 2020 (World Health Organization [WHO], 2020).
Wuhan, Hubei Province, China served as the initial epicenter of the outbreak.
Initially health officials believed that animal-to-person spread of COVID-19 first
occurred in a live seafood and animal meat market in Wuhan, China. Since then,
however, many different theories have emerged. The Centers for Disease Control (CDC)
cited likely animal to human transmission as the source of the outbreak (2020a).
Following the initial cases identified, human-to-human transmission started rapidly
occurring (CDC, 2020b). There were four long-standing human coronavirus strains that
commonly infected humans globally before COVID-19 and caused mild symptoms:
229E, NL63, OC43, and HKU1. Two more recent, and more severe, novel coronaviruses
included Middle East Respiratory Syndrome (MERS) and Severe Acute Respiratory

2
Syndrome (SARS). Both of these infections mutated and began spreading from animals
to humans, but did not spread as quickly and widely as COVID-19 had (CDC, 2020c).
Once a pandemic was declared, the CDC issued guidelines intended to slow the
spread of the virus. These guidelines included engaging in work or school activities from
home as much as possible, avoiding groups of ten or more people, maintaining a distance
of six feet away from other individuals when out in public, avoiding travel and eating at
restaurants, and avoiding visits to long-term care facilities. In addition, United States
residents were advised to stay at home if they were feeling sick, practice isolation
precautions for the entire household if anyone tests positive for COVID-19, and engage
in strict social distancing for the immunocompromised or elderly (CDC, 2020b). Some
states, including California, enacted stricter stay-at-home orders, forcing non-essential
businesses to close for a period of time and restricting public activities to only those
essential such as grocery shopping and caring for healthcare needs of humans and pets
(Executive Department, State of California, 2020). Following this order, many outpatient
healthcare agencies started limiting in-person appointments and started incorporating
telehealth on a more frequent basis.
Backgrounds
Health education is of utmost importance during a pandemic. Because worldwide
pandemics are fairly rare, there is limited information regarding community health
education strategies during pandemics. The last pandemic was the novel influenza A
H1N1 strain of 2009. Two studies performed following this pandemic, one in Malaysia
and the other in the Netherlands, demonstrated that individuals who received a greater
amount of health information were more likely to practice infection control and

3
preventive measures (Wong & Sam, 2010; Van der Weerd et al., 2011). Those with
lower levels of education preferred televised education over written educational pieces.
People interviewed also preferred education from healthcare professionals (Wong &
Sam, 2010). Both studies demonstrated that the general public favored information
regarding disease prevention and treatment (Wong & Sam, 2010; Van der Weerd et al.,
2011). Another research study in the United States demonstrated that people who
expressed higher concern and knowledge during a pandemic were more likely to engage
in preventive measures such as handwashing, social distancing, and wearing a mask. The
health practices of those of lower socioeconomic status were more likely to be influenced
by their social networks partially due to lack of access to healthcare (Lin et al., 2018).
With the institution of strict social distancing practices in California, multiple
public health needs became evident. Many people became concerned and even afraid for
their lives during the epidemic. Dissemination of information regarding preventive
measures recommended by the CDC had the potential to empower community members
and instill in them a greater sense of control over their health and wellbeing.
Smoking cessation was also an important subject of health education during this
time. A systematic review of multiple studies performed during the surge of COVID-19
cases in China noted a significantly higher chance of severe disease and death among
those who smoked. In fact, when further analysis was performed regarding the data in
one large-scale study, it was found that smokers were 1.4 times more likely to have
severe symptoms and 2.4 times more likely to require intensive care admission, require
mechanical ventilation or die than those who did not smoke (Vardavas & Nikitara, 2020,
pg. 2). There was developing evidence that vaping may potentially have been a cause of

4
increased morbidity with respiratory illnesses such as COVID-19. Vaping had recently
been found to be associated with e-cigarette or vaping product use-associated lung injury
(EVALI). EVALI often manifested as pneumonia, alveolar damage or fibrinous
pneumonitis (Ullo et al., 2020). A study involving exposure of mice to e-cigarette vapor
both with and without nicotine demonstrated delayed immune response and increased
lung inflammation when infected with influenza. The results were independent of
nicotine exposure, suggesting that the lung damage was associated with solvents in the
vaping solution itself and not nicotine (Madison et al., 2019). Because respiratory health
was an important factor in the COVID-19 pandemic, it was a relevant time to discuss
measures such as ceasing smoking and vaping to improve respiratory health both during
the pandemic and in anticipation of future respiratory illness.
The CDC reported that those with pre-existing conditions were at a higher risk for
contracting COVID-19. Many of these diseases are related to poor lifestyle practices and
could be avoided or improved with lifestyle changes. Examples included diabetes,
obesity, and cardiovascular disease (CDC, 2020d). Although prevention of COVID-19
complications through lifestyle changes during the pandemic may have been behind time,
this was a unique opportunity to educate the public on making lifestyle changes that
could prevent illness in the future.
Additionally, other public health needs had surfaced in the midst of the pandemic.
The disruption of daily routines as well as social isolation had the potential to increase
feelings of anxiety in the general population but especially in children and those with pre-
existing mental health diagnoses. Education regarding resources that were available for
individuals who were exhibiting increased mental distress as well as encouraging

5
appropriate social interaction during the pandemic proved to be helpful (Gordon, 2020).
Healthcare workers were also considered a high-risk group for mental distress and illness
during the pandemic. People who had no previous history of mental illness were also
experiencing symptoms of anxiety and depression during COVID-19. Improved access
to mental health interventions via a smartphone or the internet had the potential to
decrease morbidity and mortality related to mental illness during the COVID-19
pandemic (Cullen et al., 2020). Poison control also reported a rise in calls related to
household chemical exposures and ingestions (Sweeney, 2020). Timely information
during the pandemic also included precautionary instructions regarding safe use of
disinfectants in the home and dangers of ingesting disinfectants.
Community members and members of the Lincoln Amazing Grace Seventh-Day
Adventist church had also approached the project investigator with questions regarding
the pandemic. The church also requested that the project investigator provide some type
of online health education regarding topics relevant to COVID-19 to help educate and
empower the church members and community.
Problem Statement
There was a need for healthcare providers to provide community health education
during the time of pandemic. Many community health needs had surfaced over the time
period of the COVID-19 pandemic including a lack of focus on general health principles
such as exercise, following a healthy diet, and getting enough fresh air and sunshine; a
need or community health education on how to avoid illness or stay well during the
pandemic; and the need for dissemination of accurate health information by healthcare

6
professionals. Community and church members in the Lincoln, CA area requested
community education regarding topics relevant to the COVID-19 pandemic.
Purpose and Objectives
The purpose of this project was to fulfill the need for accurate community health
education regarding topics relevant to the COVID-19 pandemic in the Lincoln, CA area
and surrounding communities. The project evaluated the effect of a thirty-day online
community health education program on the health knowledge and self-efficacy of
participants during the COVID-19 pandemic. Project objectives included the following:
1. To evaluate the effect of online health education on the health knowledge of the
community during a pandemic utilizing a health questionnaire pre-test and post-
test.
2. To explore the association between demographic factors and community health
knowledge.
3. To determine if online health education led to increased self-efficacy during a
pandemic utilizing the General Self-Efficacy Scale as a pre-test and post-test.
PICO Questions
1. During the COVID-19 pandemic, does an online health education curriculum
improve community health knowledge?
2. During the COVID-19 pandemic, does an online health education curriculum
increase self-efficacy?
3. Do demographics such as age, gender, education level, race and healthcare
provider or not impact the effectiveness of an online health education curriculum
during the COVID-19 pandemic?

7
Impact and Significance of Project on Healthcare System and Population
The goal of this project was to identify whether online learning modules were an
effective technique for educating individuals in the community during a pandemic. This
was a nursing intervention with the potential to help influence education during the
COVID-19 pandemic and future pandemics, especially during a time when in-person and
group education was discouraged. The anticipated significance of this intervention on
the population involved them feeling empowered to take charge of their health and
prevent illness through simple daily practices.
Conclusion
Health education during a pandemic required a different strategy. In-person visits
with providers were limited and group education was not an option. Providing online
video education with health professionals regarding topics relevant to health during a
pandemic had the potential to be a method that could be used effectively both during the
COVID-19 pandemic and pandemics to come.

8
CHAPTER 2
CONCEPT IDENTIFICATION, THEORETICAL FRAMEWORK, AND
REVIEW OF LITERATURE
There were very few alive in the United States in 2019-2020 who had been
exposed to such a widespread pandemic as COVID-19. Many were faced with
challenges as they attempted to navigate through life incorporating practices that were
foreign such as minimizing in-person interaction with other individuals, maintaining
physical distance and wearing a mask. As many healthcare offices were becoming more
hesitant to schedule routine, in-person office visits and focused on emergency care and
telehealth adoption, it was vital for community members to continue to receive support
and education from healthcare professionals. The primary goals of health promotion
during a pandemic involved (1) the use of the internet as the primary means of health
education, (2) prevention of the spread of disease, and (3) maintaining optimal physical,
spiritual and mental health.
Theoretical Framework
The Health Belief Model
The Health Belief Model was developed in the 1950s by several social
psychologists working with the United States Public Health Service. During this time,
public health primarily focused on prevention of disease. As the United States Public

9
Health Service offered free programs aimed at screening for and detecting asymptomatic
disease, they found that many people did not take advantage of these services. Free chest
x-rays were offered to screen for tuberculosis; however, many did not take advantage of
this service. While the theory was first designed to help public health officials explain
why people were not taking advantage of free preventive services, it eventually was also
applied to the response patients exhibit towards symptoms and compliance with
prescribed regimens. The Health Belief Model was based on the belief that behavior, in
general, depended on (1) the value a person places on a goal and (2) the likelihood that
the goal would be achieved by a certain action. When applied to health, these variables
include (1) the desire to avoid sickness or to get well and (2) the belief that specific self-
care actions will either prevent or relieve illness (Janz & Becker, 1984).
Today, the Health Belief Model has been one of the most widely used theoretical
frameworks regarding health behaviors. The Health Belief Model described four beliefs
that help influence the readiness of an individual to take action: perceived susceptibility,
perceived severity, perceived benefits and perceived barriers (Herrmann et al., 2018).
Perceived susceptibility and severity involved the individual’s perception of threat, while
perceived benefits and barriers involved the individual’s expectations. Both of these
factors are influenced by the person’s background including demographics,
socioeconomic status, education level and past knowledge of the problem. Two other
components to the model included cues to action and self-efficacy. Fairly self-
explanatory, cues to action involved any event that inspired an individual to take action.
Examples of cues to action include the influence of friends and family, television ads or
commercials, or a medical diagnosis. Self-efficacy was added to the revised Health
10
Belief Model in the 1980s and involved confidence that an individual’s efforts would be
successful (Kim & Zane, 2016).
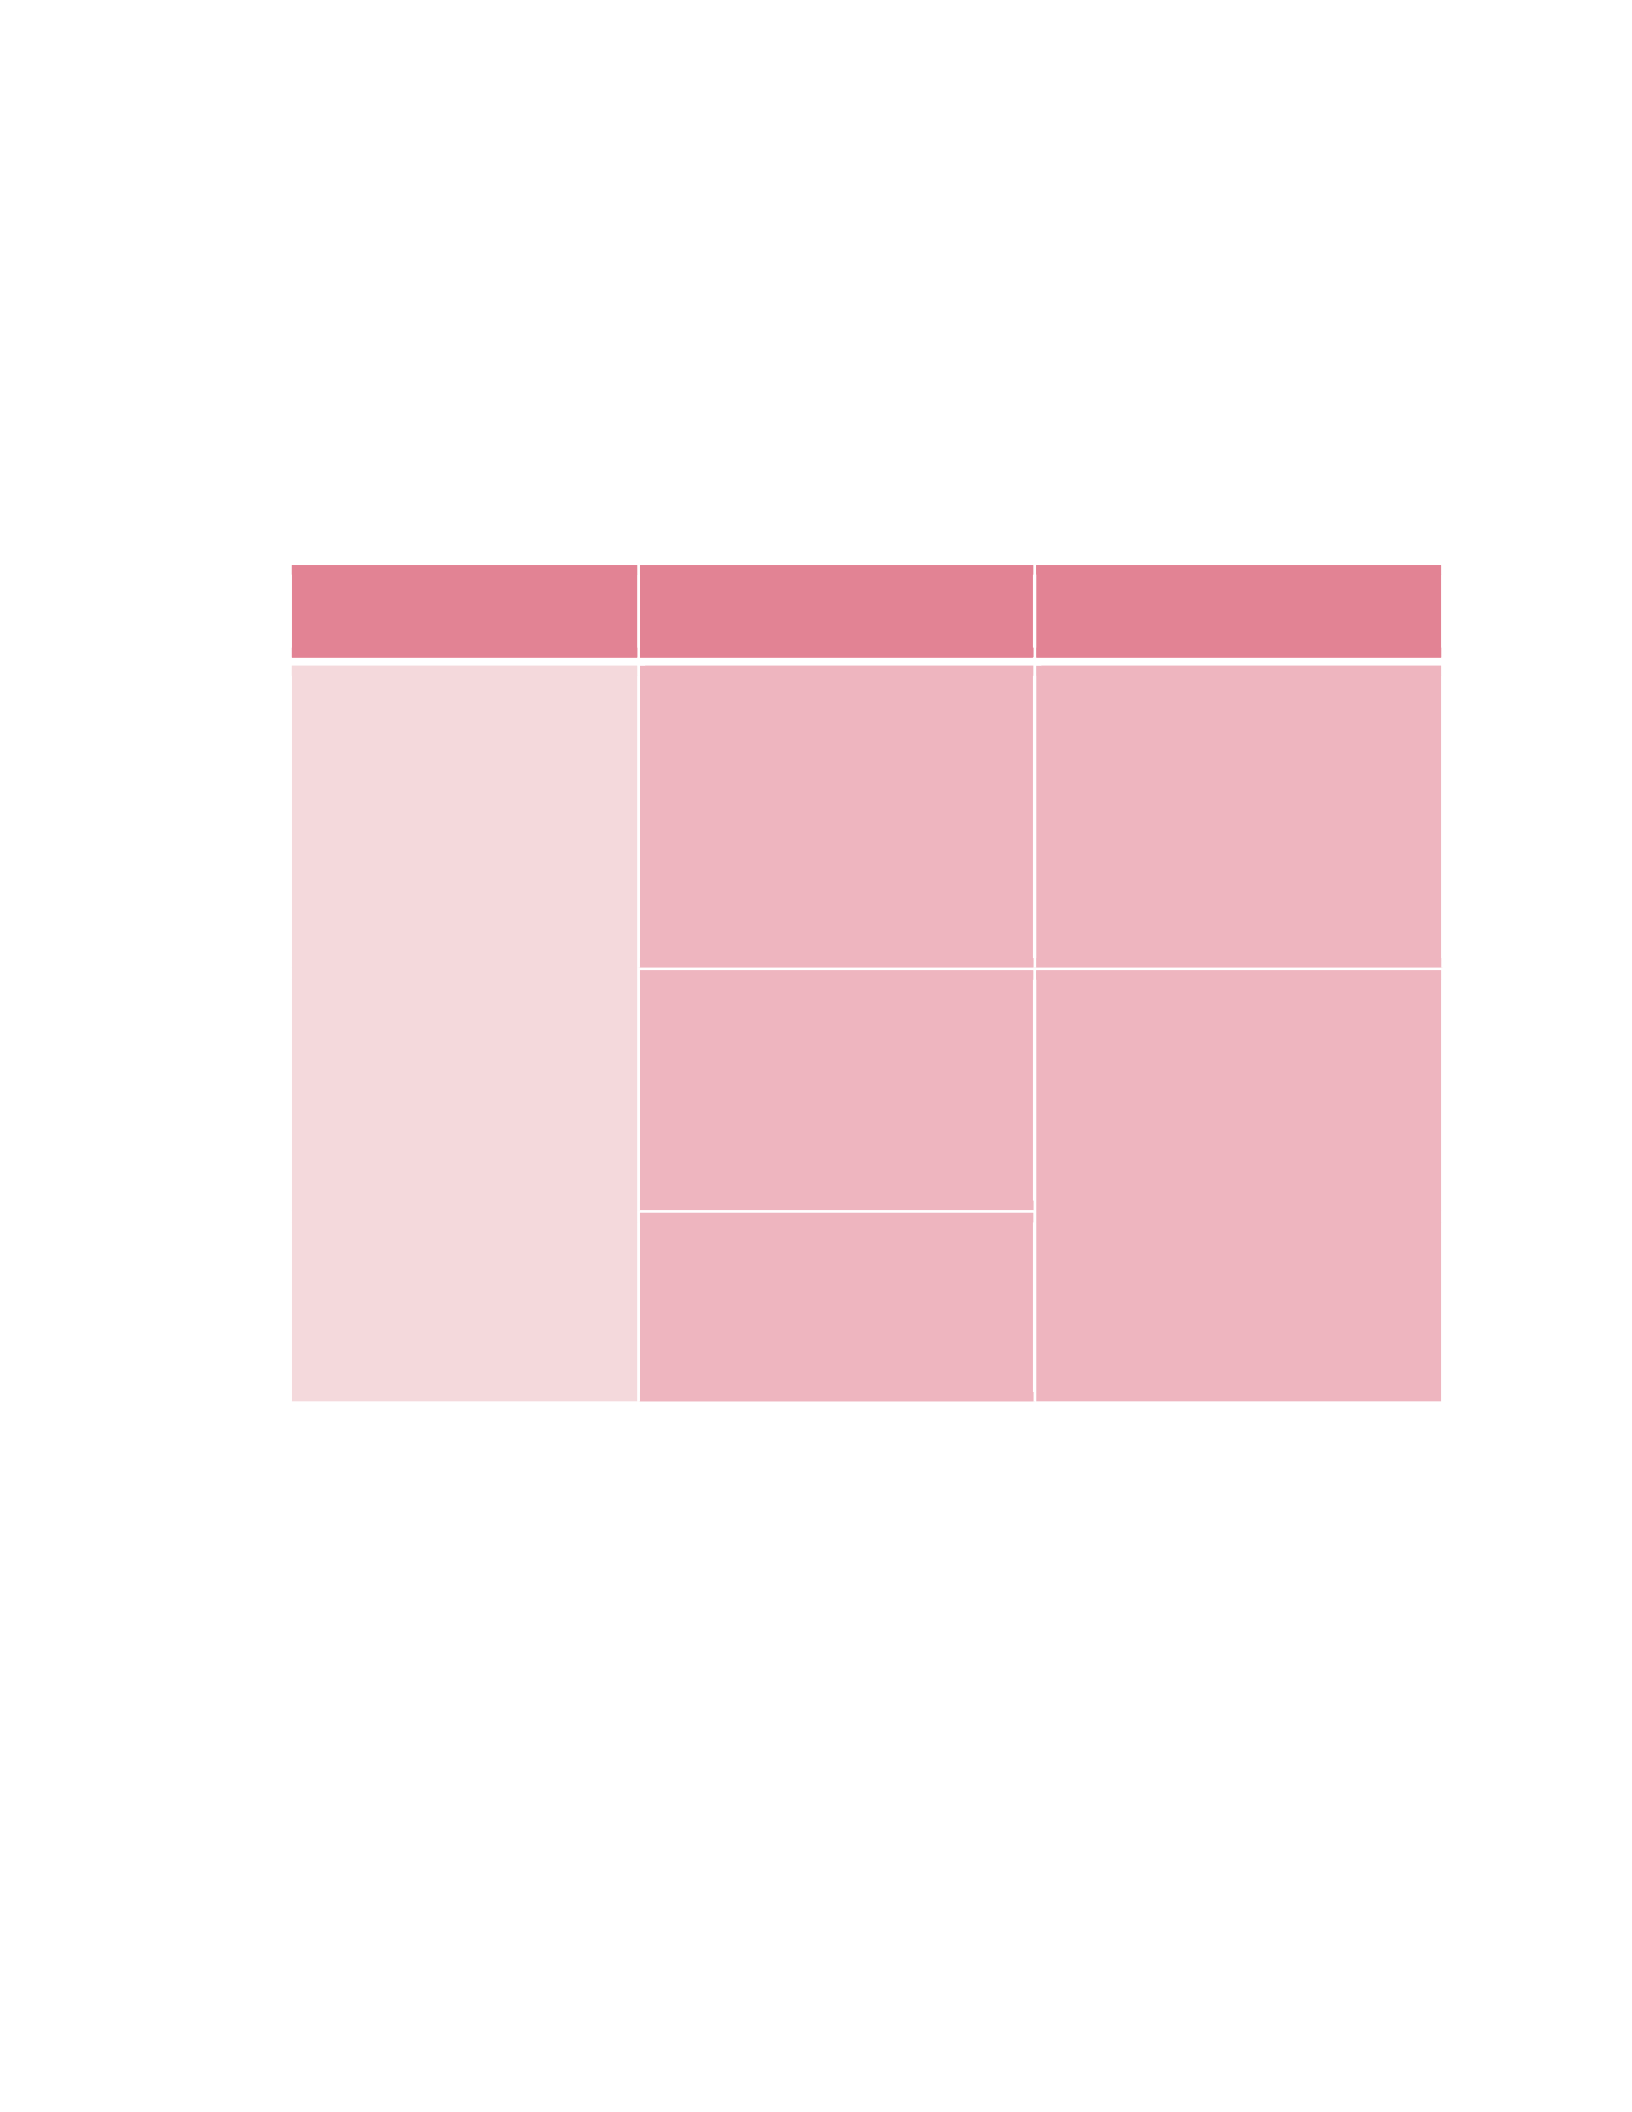
Table 1
The Health Belief Model as a Guide for an Online Health Education Curriculum
Individual Perception
Modification Factors
Likelihood of Action
Demographics
• Knowledge
• Socioeconomic
Status
• Education
• Background
Perceived Self-Efficacy
Outcomes
• Increase in
Knowledge
• Increase in Self-
Efficacy
Perceived Threat
• Perceived
susceptibility
• Perceived severity
Cues to Action
• Education
• Raised Awareness
Expectations
• Perceived Benefits
• Perceived Barriers
Note. Adapted from Rosenstock et al., (1974).
Application of Theory to Project
Application of Health Belief Model
The Health Belief Model was the primary theoretical framework utilized to
develop Renew: Better Me, Better We, an online health education program to educate
community members during the COVID-19 pandemic. The first lecture focused

11
primarily on the perceived susceptibility and perceived severity of COVID-19. Because
there had already been significant education provided to the public by the CDC, local
health agencies and news reports, the public, in general, already had a heightened sense
of susceptibility and severity; therefore, spending a significant amount of time on this
was not indicated. Many people were already wearing masks and gloves out in public,
which demonstrated an understanding to some extent regarding susceptibility and
severity. A different approach to education was something that would be welcomed by
individuals and was thought to have the potential to increase health knowledge based on
the ability to ask relevant questions and have them answered by a dedicated health
professional. During the period of the intervention, the California state governor had
already issued a statewide stay-at-home order (Executive Department, State of California,
2020). While the CDC had suggested the use of a cloth mask while out in public (CDC,
2020e), some counties in California such as San Bernardino and Riverside counties had
already taken it a step further and required that everyone wore a face covering while out
in public (San Bernardino County, 2020; City of Riverside, 2020). By the time the
intervention was already in process, the use of a cloth facemask while in public became a
statewide mandate (“Masks and Face Coverings,” 2020).
The remainder of the educational information focused on health topics relevant to
COVID-19 including mental, dental and physical health. Each lecture began with
information on susceptibility and severity and then transitioned to interventions including
benefits and barriers. For example, one lecture focused on smoking cessation. In the
beginning of the lecture, the presenter discussed how smoking affects respiratory health
in general and then incorporated data regarding the severity of COVID-19 seen in those

12
who smoked. This approach was utilized in hopes that this “cue to action” might assist
participants to recognize and acknowledge the susceptibility and severity related to
smoking. Following, methods that have shown promising results in smoking cessation
were discussed along with the benefits and barriers that came along with them.
Change in knowledge may be not be as powerful as it could be if it is not
accompanied by self-efficacy – the belief that a person can set out to accomplish a goal.
This project also aimed to evaluate whether this online health education program had an
effect on self-efficacy utilizing the General Self-Efficacy Scale which was included in the
pre-test and post-test.
The factors being measured that were linked to likelihood of action included an
increase in knowledge regarding topics pertinent to the COVID-19 pandemic using a pre-
test/post-test model and whether this health education program influenced the self-
efficacy of the participants.
Literature Review
The primary intervention for this project involved education regarding pertinent
topics related to COVID-19 delivered to community members in video form. During a
time when stay-at-home orders remained in place, online health education proved to be a
viable option for providing education in lieu of in-person health education that might
normally have taken place at office visits, classes or support groups.
Online Health Education
Online health education was a flexible way for community members to receive
information regarding health issues and could occur at any time in the comfort of their
homes. Online health education had the potential to improve self-care practices as well

13
as emotional well-being. Individuals who were able to gain knowledge often reported
feeling empowered and in control of their health, which led to decreased anxiety. Those
who understood the reason for their treatments and medications are also more likely to
adhere to them in the future (Win et al., 2015).
Research demonstrated that accurate online health education may also be
particularly important to those who did not have access to a doctor, were uninsured or
had health disparities. Young adults who were in college specifically reported that they
would rely on the internet for answers regarding their health questions. Unfortunately,
they often lacked the skills necessary to evaluate the information for validity (Rennis et
al., 2015). With the plethora of health information from a variety of sources, evidence-
based health information was needed especially for groups who turn to the internet first
when looking for health guidance.
When there was a high perceived threat to health recognized by the public, online
education became even more valuable. One study demonstrated that trust is significantly
related to adoption of health-related practices presented on social media. It also found
that trust was highly influenced by perceived knowledge, knowledge consensus and
source credibility. Lastly, as the health threat and fear increased, perceived knowledge
most heavily influenced trust which led to increased adoption of recommended healthcare
principles. During health threat and heightened fear, source credibility and knowledge
consensus became less important. Perceived knowledge, referring to the subjective
evaluation and perception of content, was the most significant indicator of trust regarding
health education on social media during health threats (Huo et al., 2018). During a
pandemic, people were more likely to view the health threat as being high and exhibit

14
fear regarding the unknown. This was a time when people were searching for health
information, and unfortunately, reportedly also had a tendency to stop relying on more
concrete evidence, such as source credibility, to determine if health information was
accurate. As people strived to increase their knowledge during a time of fear, it was
important to provide accurate, evidence-based information from trusted sources online
and on social media so that health was not placed in further jeopardy by adopting
potentially harmful practices.
Online health education could be utilized in conjunction with care from the
patient’s healthcare team in order to increase evidence-based practices. One study
evaluated the effectiveness of an online pre-conception healthcare module in facilitating
discussion regarding reproductive health with a healthcare practitioner. Secondary goals
included discussion of folic acid supplementation, contraception methods and self-
efficacy scores. This study involved 292 participants split between an intervention and
control group. Each group took a pre-assessment survey followed by an email with
educational curriculum. Following the next visit with the participant’s women’s health
provider, a post-assessment was performed. There was a statistically significant increase
in the number of women in the treatment group who reported discussing reproductive
care with their physicians (Batra et al., 2018). This study demonstrated that online
health education had the potential to encourage individuals to acknowledge potential
problems and then seek out solutions in conjunction with their healthcare provider.
Online health education also proved beneficial for parents when learning about
the health challenges of their children. One study evaluated the use of an online
educational website and app that targeted fathers with children who had type 1 diabetes.

15
The fathers were interviewed and filled out a questionnaire at the beginning of the study.
Following, they were provided with access to the website and/or app which included
educational topics and videos regarding diabetes management, insulin administration,
glucose monitoring, ketone monitoring, psychosocial effects, et cetera. All of the content
was written at the sixth-grade level or below. Some videos were hosted on the YouTube
site. This study found that commercial-free content and links to scientific sources helped
to gain parental trust in online health information (Albanese-O’Neill et al., 2019).
Online health education not only could be provided to the public, but also could
be beneficial for healthcare providers. British Columbia’s Provincial Health Services
Authority hosted a class regarding hepatitis C that could either be performed in person or
online. The course was available to both healthcare providers and patients. There were
312 providers and 94 patients that completed the pre-test/post-test and education. The
increase in knowledge between the in-class and online participants was comparable,
showing a statistically significant increase in knowledge following the intervention
(Buller-Taylor et al., 2018). Not only could online education provide much needed
health education to patients and the community, it had the potential to be beneficial to
healthcare providers as well.
Online health education may be developed for a generic audience or target a
specific group or city. One study evaluated an online health education website entitled
GetHealthyHarlem that was specifically designed to target the residents of Harlem, New
York. The website was developed after performing multiple interviews and focus groups
to discuss the culturally specific needs to the residents of Harlem, New York. A core
group of community members met monthly to discuss the design of the website. It was

16
launched in 2008 and then modified and relaunched in 2011-2012. During this time, the
website was being used as an intervention in a research study regarding awareness and
control of hypertension. Because of this, there was significant content on hypertension.
They also included a “healthy tip of the week” as well as shared inspiring stories of
community members (Smith et al., 2015).
Advertisement and promotion of the website was performed through the group’s
Facebook page, distribution of flyers, and community events including a photo contest
and outdoor reception. The group used Google Analytics and Facebook Insights to track
visits to the site. Following the relaunch of the site, the group was totaling 5,284 visits to
the website per month with 25%-30% returning visitors (Smith et al., 2015, pg. 483).
There was little conversion of passive to active users following the relaunch of the
website. Although there are many limitations to this study based on the methods of
evaluation, the goal of the project was to increase awareness regarding the website, drive
online traffic and establish a presence as a reputable source for health information and
those goals were met (Smith et al., 2015).
Conclusion
The Health Belief Model was demonstrated to be a sufficient guide to the
development of an online health education program for community members regarding
topics relevant to COVID-19. Online health education has been demonstrated in the
literature to be an effective method of education for the public and healthcare
professionals in previous research projects and studies. The project investigator chose to
utilize the Health Belief Model in the design of the curriculum for an online health
intervention that was entitled Renew: Better Me, Better We. This curriculum had a

17
specific focus on personal and community health with the understanding that a person’s
knowledge and self-efficacy both affect his willingness and ability to engage in
preventative health actions.

18
CHAPTER 3
METHODOLOGY
Project Design
This project utilized a quantitative quasi-experimental pre-test/post-test design
from a convenience and snowball sample. A pre-test and post-test were performed to
measure the effectiveness of an online, 30-day, nurse led, health educational intervention
entitled Renew: Better Me, Better We. The curriculum for the intervention was
developed by the project investigator with assistance from the committee chair and
members and included topics relevant to the COVID-19 pandemic including physical and
mental health topics. A pre-test was performed which included demographic information,
the Health Knowledge Assessment Questionnaire (25 questions) developed by the project
investigator and the General Self-Efficacy Scale (10 questions) developed by Matthias
Jerusalem and Ralf Schwarzer (Schwarzer, 2014). These same two tests were
administered post-intervention. SurveyMonkey was utilized as a platform to administer
the pre-test and post-test. Each participant who fully completed the research project was
provided with an electronic Amazon gift card in the amount of $10.00 as a thank you for
their participation.

19
Population and Sample
The project investigator worked in cooperation with the Lincoln Amazing Grace
Seventh-Day Adventist Church. Because of this, the research project primarily focused
on the members and contacts of the church as well as residents in the surrounding
communities. Church members and approximately 900 community members who had
expressed interest in community programs were invited to join the program utilizing an
approved script and flyer. Targeted Facebook advertising was primarily used to invite
those in the community to join the research project. Because this research project
includes snowball sampling, anyone could invite others to join the project.
Independent and Dependent Variables
The independent variable in this research project was COVID-19 health
education. Dependent variables included health knowledge and self-efficacy.
Sample Size
The paired t-test was utilized to estimate sample size assuming a medium effect,
an alpha of 0.05 and a power of 0.80. The recommended sample size was 34 to control
for attrition. The project investigator, however, aimed to include at least 50 participants.
Utilizing the aforementioned recruiting methods, a total of 66 participants consented to
participate in the project by taking the pre-test through SurveyMonkey. Because the
attrition rate was noted to be fairly high once the first cohort began the intervention, a
second period of recruitment was performed which resulted in a second and very small
third cohort. A total of 45 participants in total completed the entire project including the
pre-test, watching the health videos, and taking the post-test. Because the only means of
contact was an email address, it was difficult to maintain contact with the participants.

20
The project investigator did send reminder emails to participants who stopped watching
the video presentations in hopes of encouraging them to complete the research project.
Some responded noting that they did not receive the episode. If this was the case, the
episode was resent. Others responded by resuming watching the episodes and others did
not reply.
Definition of Participation
Participation in the research project was defined by the following criteria:
• Having consented to participate in the research project by submitting the pre-tests
o Health Knowledge Assessment Questionnaire
o General Self-Efficacy Scale
o Demographic Information
• Having watched the Renew: Better Me, Better We health education curriculum
o Eight video presentations that are approximately 10 minutes each
o Link to each presentation were sent to provided email address
o Video presentations were posted on Panopto to monitor which participants
were viewing the presentations and for how long
• Submitted the post-tests within two (2) weeks of receiving the link via email.
o Health Knowledge Assessment Questionnaire
o General Self-Efficacy Scale
o Demographics
• Provided email address to account for accurate tracking of pre-test and post-test
results.
• Email address was used to send links to lectures and post-tests

21
• Each participant who successfully completed each of these steps received an
electronic Amazon gift card in the amount of $10.00.
Inclusion and Exclusion Criteria
Inclusion criteria included that each participant be either male or female and was
an adult of at least 18 years of age. Additionally, each participant was required to have
access to a computer, smartphone or tablet in order to access the pre-test, health lectures
and post-test via the internet. Multiple participants within the same household were
allowed, however, the pre-test and post-tests were to be completed independently.
Recruitment
Members and contacts of the Lincoln Amazing Grace Seventh-Day Adventist
Church received an email utilizing an approved script inviting them to participate in the
project. Each of the aforementioned individuals were also mailed an approved flyer with
information regarding the research project. The same flyers were also placed in food
bags during the weekly community food giveaway at Lincoln Amazing Grace Seventh-
Day Adventist Church. An approved Facebook page entitled Renew: Better Me, Better
We was developed and utilized in Facebook targeted advertising to the following zip
codes: 95658, 95648, 95765, 95663, 95650, 95602, 95603, 95604. Participants and
anyone interested in the research project were also given permission to refer others who
were interested in participating in the research project to the Facebook or SurveyMonkey
page.
Following Project Participants
The only personal information that participants were required to provide was an
email address. The purpose of including the email address was to provide a means for

22
the project investigator to be able to match pre-test and post-test and as a means of
communication during the intervention period. Each email address was assigned a
participant identification (ID) number in order to de-identify the data. The participant ID
number was utilized in the participant tracking log by the project investigator to track
tasks related to the project. The tracking log that was developed included the following
information for each participant ID number:
• Implied consent/pre-tests submission
• Whether each Renew: Better Me, Better We lecture was watched and now many
minutes were watched
• Submission of post-tests
• Electronic delivery of $10.00 Amazon gift card after completing all steps outlined
in the definition of participation.
23
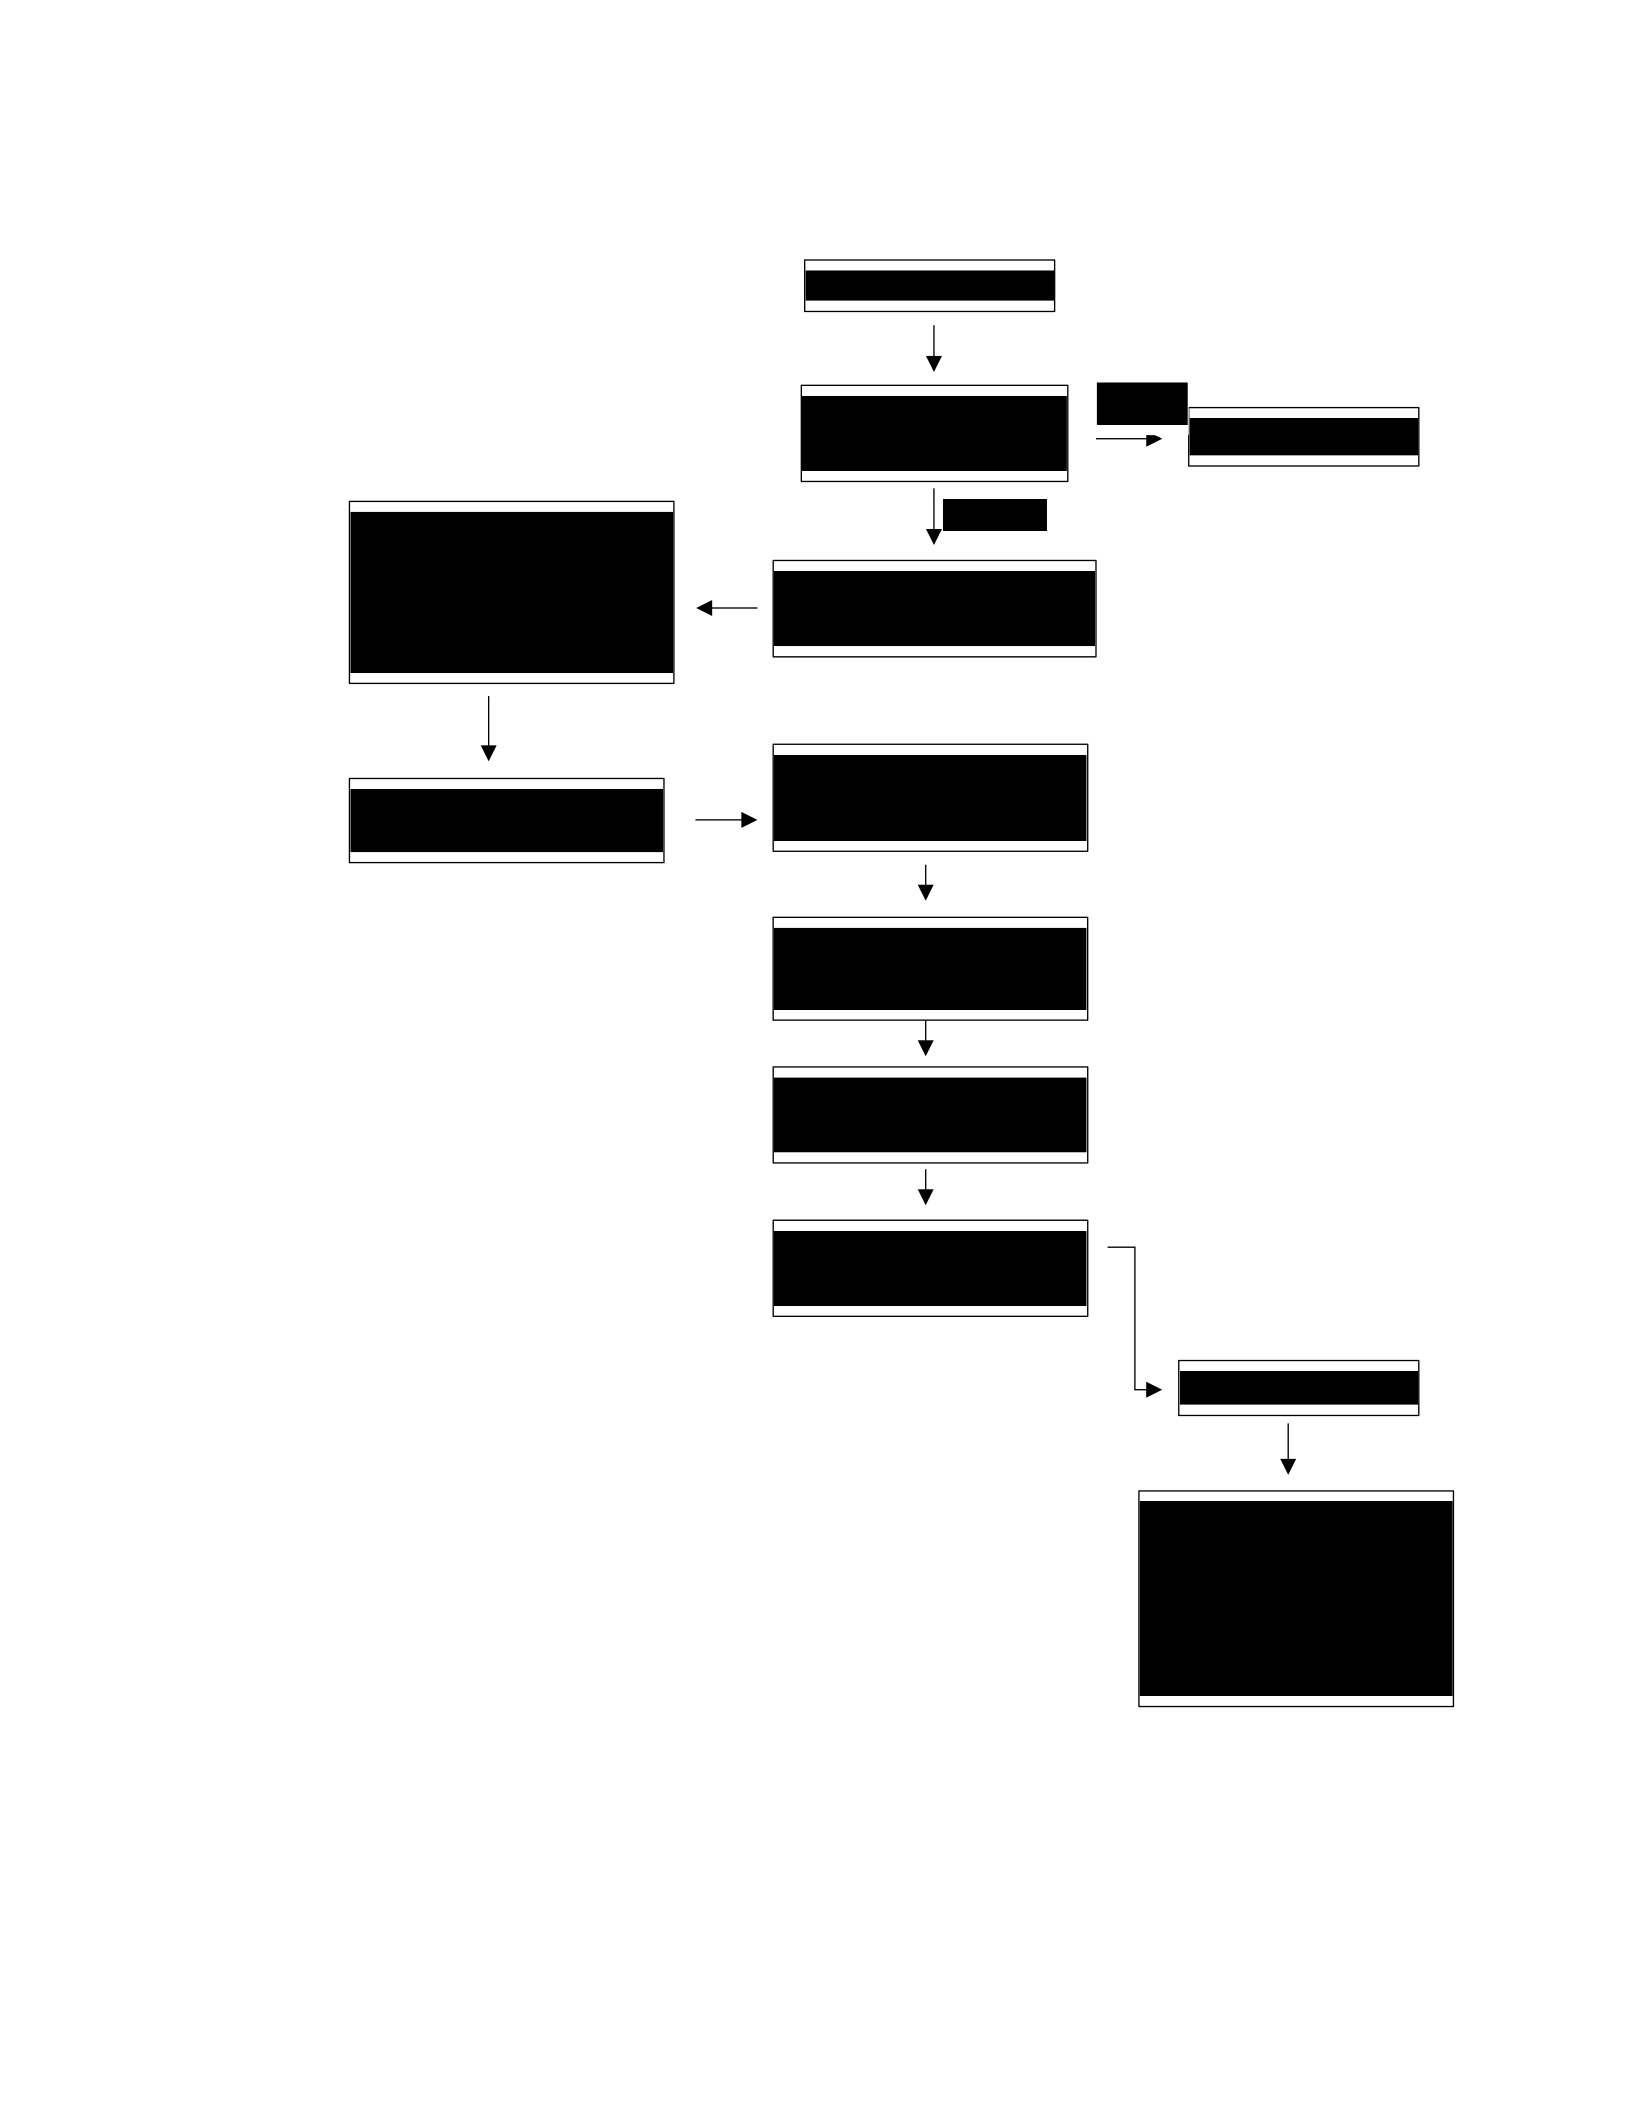
Figure 1. Project Protocol
Recruitment
Participant
Screened In
Thank you
Consent and Take
Pre-Test
Cohort 1, n=36
Cohort 2, n=27
Cohort 3, n=3
Total Enrolled, n=66
Week 1 – Received
Videos 1 and 2
Week 2 – Received
Videos 3 and 4
Week 3 – Received
Videos 5 and 6
Week 4 – Received
Videos 7 and 8
Begin Intervention
Take Post-Test
Cohort 1, n=25
Cohort 2, n=19
Cohort 3, n=1
Total Completed,
n=45
No
Yes

24
Measurement/Instrumentation
The 25-question Health Knowledge Assessment Questionnaire created by the
project investigator was developed in conjunction with the health education curriculum.
There were at least two questions on the questionnaire related to each topic covered in the
curriculum. The questionnaire was reviewed by the committee chair and committee
members for accuracy and clarity. This team had a diverse education background
including a Ph.D., master’s in public health (MPH) and medical doctor (M.D.).
Additionally, the project investigator asked two community members to answer the
questions on the questionnaire and provide feedback. The wording of several questions
was changed/clarified in response to the feedback received. The test consisted of
multiple choice, select all that apply and true/false questions with a possible score
ranging from 0-25/25. The primary investigator had chosen to regard a score of 70% as
“knowledgeable.” Additionally, the primary investigator’s goal for practical significance
was to note an increase of between 10-20% in post-test scores, the difference of one to
two letter grades.
The General Self-Efficacy Scale was a tool developed by Matthias Jerusalem and
Ralf Schwarzer. It was a self-reported self-efficacy assessment consisting of 10
questions with a possible score of 10-40/40 with lower scores being indicative of lower
self-efficacy and higher scores being indicative of higher self-efficacy. The tool was
proven to be reliable with a Chronbach’s alpha between 0.75-0.91 (Scholz et al., 2002,
pg. 243). The scale was utilized in several large-scale research studies that have
confirmed its validity. The General Self-Efficacy Scale showed consistent, positive
correlation with optimism, pro-active coping, self-regulation, perception of challenge in

25
stressful situations and perception of expected social support; likewise, there was
consistent negative correlations associated with depression, anxiety, burnout,
procrastination, and lack of accomplishment. Additionally, it was shown to be
unidimensional (Schwarzer et al., 2000). Scoring for each question ranged from one to
four (1=not true at all, 2=hardly true, 3=moderately true, and 4=exactly true). The
General Self-Efficacy Scale was available to be used without permission in research
studies (Schwarzer, 2014).
The Renew: Better Me, Better We health education curriculum was developed by
the project investigator and presented by the project investigator and committee member
Anil Kanda, MPH. Each presentation ranged from 10-12 minutes in length and was
posted on Panopto for participants to watch. There was a total of eight presentations,
with two posted to Panopto per week for a total of four weeks. Participants were notified
via their provided email address when each presentation was available. The Panopto
hosting site allowed for the primary investigator to assess data including which
participants had watched the presentations, how many minutes they watched, and if any
part of the presentation was watched more than once.
The Renew: Better Me, Better We curriculum was guided by the Health Belief
Model. The topics covered were relevant to the COVID-19 pandemic and included the
following topics: an overview of COVID-19, information regarding healthy nutrition
practices and hydrotherapy to strengthen the immune system, discussion regarding safe
use of disinfectants in the home, tips for maintaining mentally healthy during the
pandemic, improving respiratory health, and how COVID-19 was specifically affecting
children (Table 2). Each lecture discussed the perceived susceptibility, perceived

26
severity, perceived threats and perceived benefits of each topic and intervention. The
importance of self-efficacy was incorporated by discussing simple techniques related to
each topic. The Renew: Better Me, Better We intervention was employed as a cue to
action in hopes of educating those participating regarding pertinent topics and promoting
increased health awareness. The expected outcomes included an increase in health
knowledge and self-efficacy as measured using the aforementioned post-test.

27
Table 2
Researcher-Developed Community Health Education Intervention Topics/Content
Renew: Better Me, Better We
Included Content
1. COVID-19 Overview
Presenter: Kerstin Ashby Ferguson
● What Is It?
● Is it really worse than the flu?
● Protecting myself and loved ones
● Current testing guidelines
2. Self-Care and a Pandemic: Keeping Healthy
When Doctors’ Offices Are Closed
Presenter: Anil Kanda
● Nutrition ● Vitamins & Supplements
● Sunshine ● Wearing PPE
3. Self-Care and a Pandemic: Keeping Healthy
When Dentist Offices Are Closed
Presenter: Kerstin Ashby Ferguson
● Dental Hygiene
● Links to immune system
● Dental Hygiene & Links to overall
health
4. Increasing Your Body’s Own Ability to
Fight
Presenter: Anil Kanda
● Benefits of Hydrotherapy on the
immune system
5. Safety First: Use of Disinfectants in the
Home
Presenter: Kerstin Ashby Ferguson
● What if I cannot find antibacterial
products?
● Dangers of mixing disinfectants
● Poison control education
6. Improving Respiratory Health
Presenter: Kerstin Ashby Ferguson
● Smoking & COVID-19 severity
● Vaping associated morbidity
● Strategies for smoking cessation
● Where to go to get help
7. Interventions for Maintaining Mentally
Healthy During a Pandemic
Presenter: Anil Kanda
● Current research ● Balanced diet
● Exercise
● Deep breathing & Exercise
● Spiritual health
8. COVID-19 & Children
Presenter: Kerstin Ashby Ferguson
● Infection rates
● How children respond to change
● Helping children cope

28
Confidentiality
All data was de-identified utilizing participant ID codes prior to analysis. The
participant log, which was a record of matched emails to participant ID codes, was stored
on the project investigator’s password protected computer in a file separate from any de-
identified data collection files. Email addresses were only used by the project
investigator to communicate with participants during the research period. The email
addresses were not shared or used for any other purpose.
Data collection was obtained utilizing SurveyMonkey. IP tracking was disabled
in order to allow for greater security and to make it easier for multiple members of the
same household to participate. According to SurveyMonkey, their data is stored in SOC
2 accredited data centers and is transmitted over a secure HTTPS connection. Data at rest
was encrypted per the industry standard (SurveyMonkey, 2020).
Internal/External Validity
Factors associated with this research project that improved internal validity
included experimental manipulation utilizing the independent variable and adhering to
the study protocol as to avoid variation in data collection and intervention
implementation. The same instrument was also used to collect pre-test and post-test data.
Threats to external validity were decreased by incorporating a broad inclusion
criterion, allowing for the characteristics of the sample to be as close as possible to the
characteristics of the population. Demographic data was collected and used to further
analyze whether demographics had an effect on the knowledge of participants.

29
Implementation
This project began with a two-week period of recruitment utilizing the
aforementioned strategies including Facebook targeted advertising, recruitment from the
Lincoln Amazing Grace Seventh-Day Adventist church and through word of mouth by
other interested parties. The Renew: Better Me, Better We Facebook page was activated
and advertising started on May 14, 2020. Additionally, the communications committee
for the church distributed an informational flyer via mail and email to its members and
contacts as well as distributed flyers in food bags provided to the community during their
weekly food giveaway. During this period, potential participants were able to view
information regarding the research project by navigating to the cover page of the pre-test
utilizing the SurveyMonkey link or the project Facebook page. The SurveyMonkey
cover page incorporated all of the required elements of informed consent. Those who
chose to participate were also able to take the pre-test after submitting the consent form.
Those who chose not to participate were able to either select “no” at the bottom of the
consent page, or simply close their browser. Each participant was required to provide an
email address as part of the pre-test process.
The pre-test consisted of the 25-question Health Knowledge Assessment
Questionnaire developed by the project investigator, 10-question General Self-Efficacy
Scale, and demographic questions. All questions required an answer.
The first cohort of participants involved 36 people who submitted the pre-test.
The first Renew: Better Me, Better We episode was produced by the project investigator
and submitted to participants via Panopto on May 28, 2020. Following, the participants
received a new episode every Tuesday and Friday thereafter for the duration of the eight

30
episodes. Each time an episode was available, each participant would receive an email
from the project investigator’s university email address containing details on how to
access the new episode as well as an email generated from Panopto with a direct link to
the video.
Because the attrition rate was found to be high, a second period of recruiting
utilizing targeted Facebook advertising to the same zip codes was initiated on June 12,
2020. A second cohort of 27 individuals started the Renew: Better Me, Better We
intervention on June 16, 2020 and a smaller, third cohort of 3 people started the
intervention on June 23, 2020. These cohorts followed the same pattern of receiving a
new episode each Tuesday and Friday with accompanying emails over the course of four
weeks. Following the release of the last episode, the link for the post-test was emailed to
each of the participants. The post-test questions were identical to the pre-test questions.
The participants were expected to submit the post-tests within two weeks of receiving the
post-test link.
Each participant who successfully completed the entire research project was
provided with a thank you gift in the form of an electronic Amazon gift card valued at
$10.00. This gift was emailed to the email address that was provided upon submission of
the pre-test and within two weeks following the deadline for submission of the post-test.
Ultimately a total of 45 participants successfully completed the research project.
Research Project Timeline
Table 3 below outlines the research project timeline from start to finish.

31
Table 3.
Timeline for Project Start to Finish
Date
Event
May 14-27, 2020
• Recruit participants, participants take pre-tests
May 28, 2020
• Release of Renew: Better Me, Better We
episode 1, “COVID-19 Overview” (cohort 1)
June 2, 2020
• Release of Renew: Better Me, Better We
episode 2, “Self-Care and a Pandemic:
Keeping Healthy When Doctor’s Offices Are
Closed” (cohort 1)
June 5, 2020
• Release of Renew: Better Me, Better We
episode 3, “Self-Care and A Pandemic:
Keeping Healthy When Dentist Offices Are
Closed” (cohort 1)
June 9, 2020
• Release of Renew: Better Me, Better We
episode 4, “Increasing Your Body’s Own
Ability to Fight” (cohort 1)
June 12, 2020
• Release of Renew: Better Me, Better We
episode 5, “Safety First: Use of Disinfectants
in the Home” (cohort 1)
• Second wave of recruiting via Facebook
June 16, 2020
• Release of Renew: Better Me, Better We
episode 6, “Improving Respiratory Health”
(cohort 1)
• Release of Renew: Better Me, Better We
episode 1, “COVID-19 Overview” (cohort 2)
June 19, 2020
• Release of Renew: Better Me, Better We
episode 7, “Interventions for Maintaining
Mentally Healthy During A Pandemic”
(cohort 1)
• Release of Renew: Better Me, Better We
episode 2, “Self-Care and a Pandemic:
Keeping Healthy When Doctor’s Offices Are
Closed” (cohort 2)
June 23, 2020
• Release of Renew: Better Me, Better We
episode 8, “COVID-19 & Children” (cohort 1)
• Release of Renew: Better Me, Better We
episode 3, “Self-Care and A Pandemic:
Keeping Healthy When Dentist Offices Are
Closed” (cohort 2)
• Release of Renew: Better Me, Better We
episode 1, “COVID-19 Overview” (cohort 3)
June 26, 2020
• Post-test invitation email sent to participants
(cohort 1)

32
Table 3 – Continued
• Release of Renew: Better Me, Better We
episode 4, “Increasing Your Body’s Own
Ability to Fight” (cohort 2)
• Release of Renew: Better Me, Better We
episode 2, “Self-Care and a Pandemic:
Keeping Healthy When Doctor’s Offices Are
Closed” (cohort 3)
June 30, 2020
• Release of Renew: Better Me, Better We
episode 5, “Safety First: Use of Disinfectants
in the Home” (cohort 2)
• Release of Renew: Better Me, Better We
episode 3, “Self-Care and A Pandemic:
Keeping Healthy When Dentist Offices Are
Closed” (cohort 3)
July 3, 2020
• Release of Renew: Better Me, Better We
episode 6, “Improving Respiratory Health”
(cohort 2)
• Release of Renew: Better Me, Better We
episode 4, “Increasing Your Body’s Own
Ability to Fight” (cohort 3)
July 5, 2020
• Deadline to submit post-test (cohort 1)
July 7, 2020
• Release of Renew: Better Me, Better We
episode 7, “Interventions for Maintaining
Mentally Healthy During A Pandemic”
(cohort 2)
• Release of Renew: Better Me, Better We
episode 5, “Safety First: Use of Disinfectants
in the Home” (cohort 3)
July 10, 2020
• Release of Renew: Better Me, Better We
episode 8, “COVID-19 & Children” (cohort 2)
• Release of Renew: Better Me, Better We
episode 6, “Improving Respiratory Health”
(cohort 3)
July 14, 2020
• Post-test invitation email sent to participants
(cohort 2)
• Release of Renew: Better Me, Better We
episode 7, “Interventions for Maintaining
Mentally Healthy During A Pandemic”
(cohort 3)
July 17, 2020
• Release of Renew: Better Me, Better We
episode 8, “COVID-19 & Children” (cohort 3)
July 19, 2020
• Deadline for project investigator to email
Amazon $10.00 gift cards to participants
(cohort 1)

33
Table 3 – Continued
July 22, 2020
• Post-test invitation send to participants
(cohort 3)
July 23, 2020
• Deadline to submit post-test (cohort 2)
July 30, 2020
• Deadline to submit post-test (cohort 3)
August 6, 2020
• Deadline for project investigator to email
Amazon $10.00 gift cards to participants
(cohort 2)
August 13, 2020
• Deadline for project investigator to email
Amazon $10.00 gift cards to participants
(cohort 3)
August-October, 2020
• Data Analysis and write-up
Data Collection
Pre-test and Post-test values were collected through SurveyMonkey utilizing the
Health Knowledge Assessment Questionnaire and the General Self-Efficacy Scale.
Data Analysis
Pre-test and post-test data were transferred from SurveyMonkey to Microsoft
Excel. Following de-identification, the final data set was cleaned and analyzed utilizing
IBM SPSS Statistics for Windows (version 27) with a significance level of 0.05. The
paired t-test was utilized to compare the overall pre-test and post-test scores on both the
health knowledge questionnaire and the General Self Efficacy Scale in order to determine
if the intervention (Renew: Better Me, Better We curriculum) had a statistically
significant effect on health knowledge related to COVID-19 and general self-efficacy.
The project investigator had planned to use the independent t-test and one-way analysis
of variance (ANOVA) to compare mean pre-test and post-test scores within demographic
groups; however, some of the data was not of a normal distribution after recoding for
comparison. ANOVA was utilized to compare age groups and the Mann-Whitney U test
and Kruskal-Wallis test were utilized when variables were not normally distributed.

34
The project investigator believed that it was important to include healthcare
workers in the research because of their varying degrees of education regarding COVID-
19; thus, any healthcare worker could benefit from an education program like this. The
project investigator planned to compare the healthcare workers and non-healthcare
workers groups in order to determine if healthcare workers had a greater health
knowledge regarding COVID-19 when compared to non-healthcare workers, however,
only five of the 45 participants identified themselves as healthcare workers. Because of
the small sample size of healthcare workers, this comparison was not performed.
The majority of the participants watched each health video in its entirety one time.
Although the project investigator initially planned to compare results between level of
participation, this was not possible due to the lack of variation in participation data.
Conclusion
This project included a simple methodology, however, the potential for influence
in the community health education field in the future is significant. The project aimed to
demonstrate that online health education during a pandemic is associated with increased
health knowledge and self-efficacy. The results of this project had the potential to
increase quality of life during and after the intervention.

35
CHAPTER 4
FINDINGS AND RESULTS
This research project was a nurse led, educational intervention with the goal of
determining whether an online educational program related to COVID-19 had the
potential to increase the health knowledge of participants as well as to increase their self-
efficacy. This chapter provides a description of the project results including a discussion
of the data analysis and demographics of the participants. For parametric tests, the mean
(M) and standard deviation (SD) are reported and for non-parametric test, the median
(Mdn) and range. All reported p-values are single tailed.
Participant Demographics
There was a total of 45 participants who completed the project. The majority
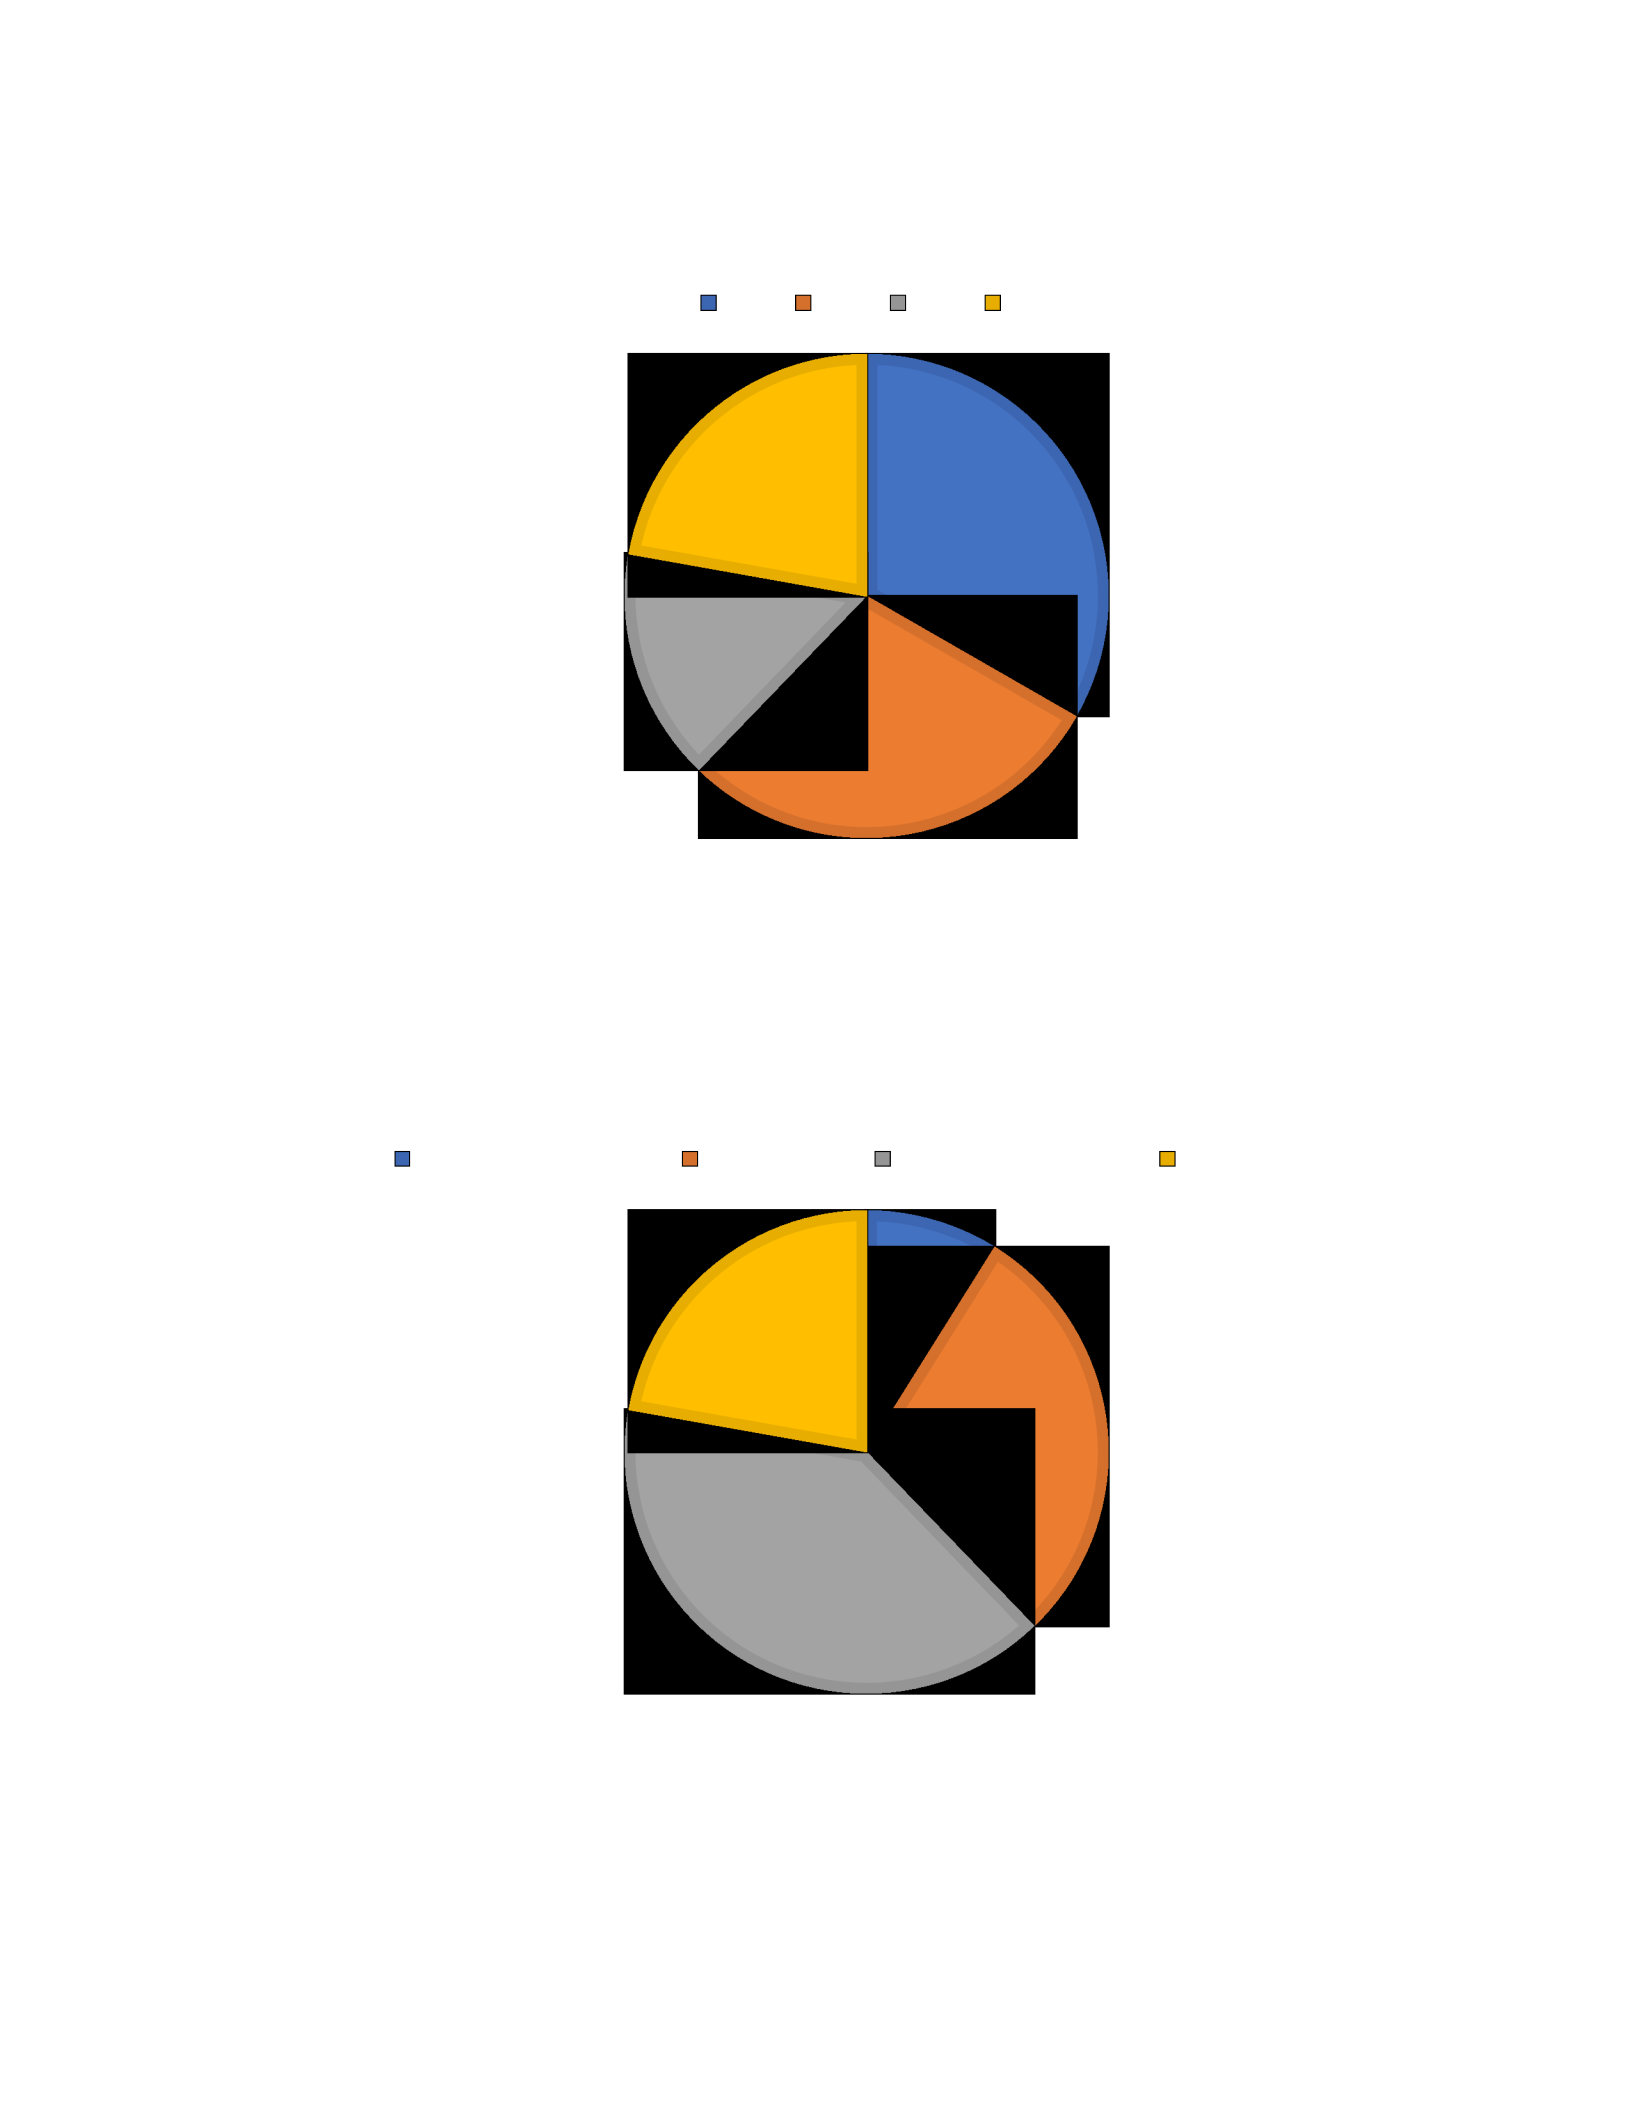
(73%) of the participants were female (Figure 2). The average age of participants was 38
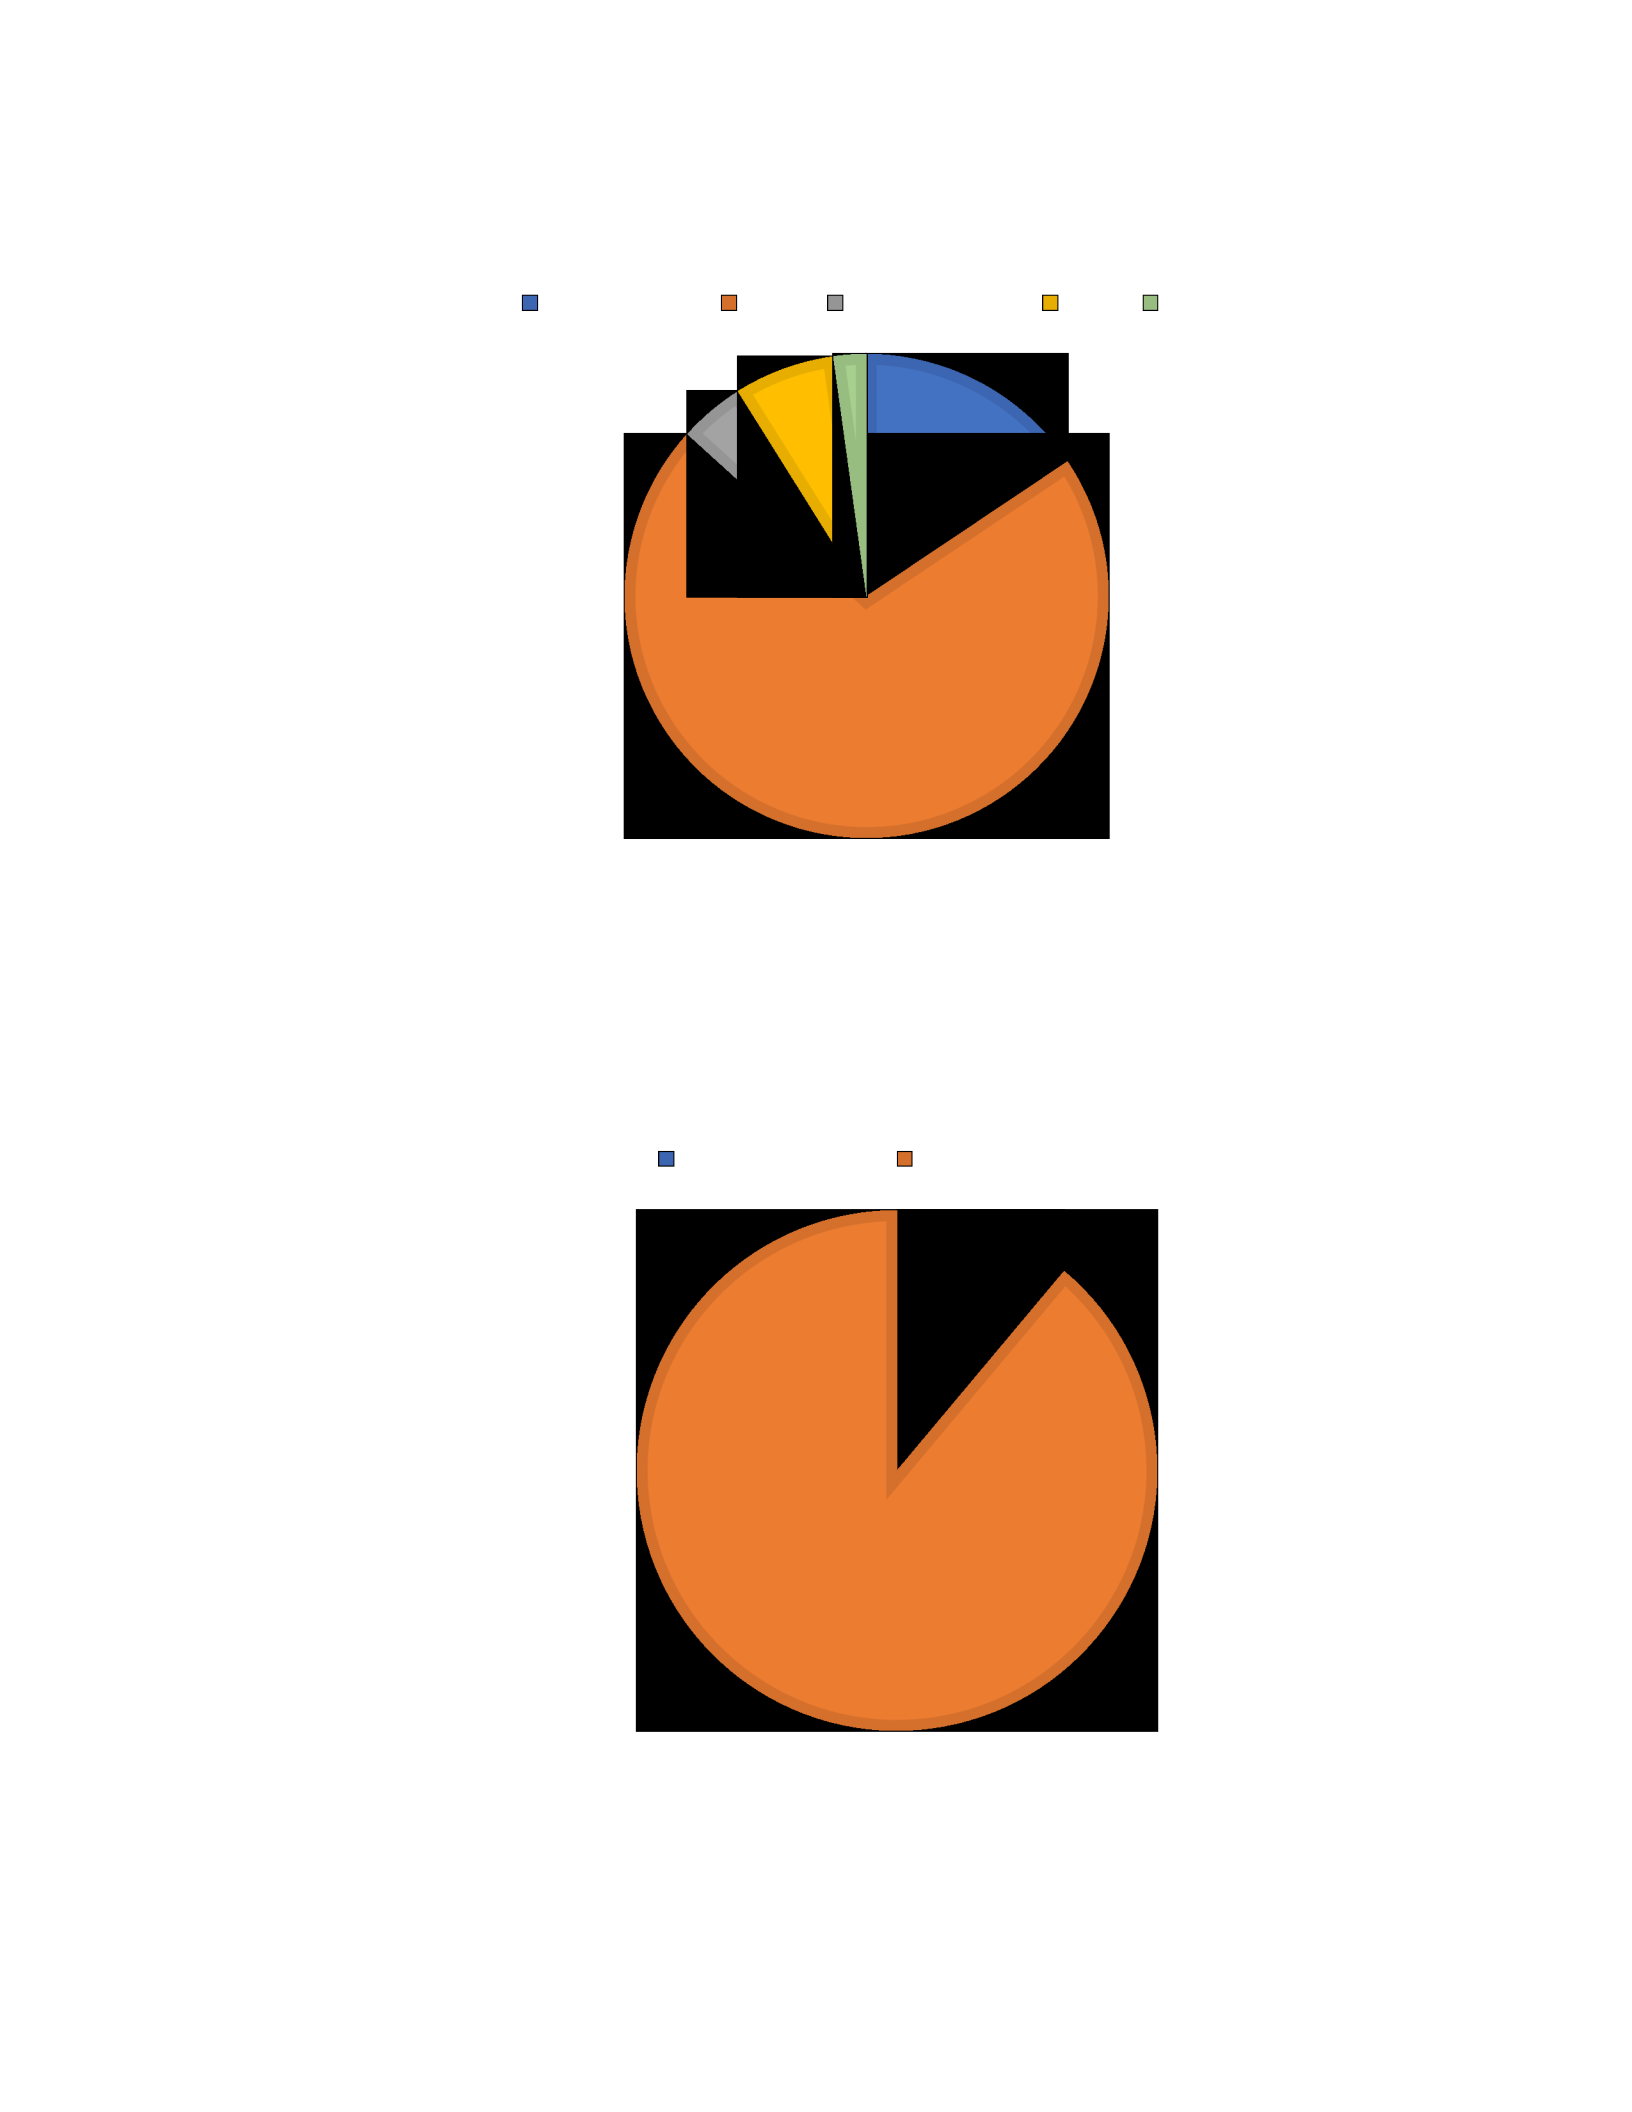
years old with the majority of participants being in the 18-29 and 30-39 age ranges, 33%
and 29% respectively (Figure 3). The most common education levels were “some
college” or “undergraduate degree” (Figure 4). Seventy-one percent of participants were
white and 89% of participants were not defined as healthcare workers (Figure 5 & Figure
6). Because of the lack of healthcare workers participating in the study, comparison
between healthcare workers and non-healthcare workers means scores could not be
performed. There was a total of 32 participants who classified their race as white and 13
participants who classified their race as African American, Hispanic/Latino, Asian or

36
other (Figure 5). Due to the smaller sample size, the race variable was recoded for
analysis to compare white participants with all other races combined. The majority of
participants classified their education level as either some college, undergraduate degree
or graduate degree. The education variable was also recoded to compare the three
aforementioned education categories.
Figure 2. Gender of Project Participants
27%
73%
GENDER DISTRIBUTION OF PROJECT PARTICIPANTS
Male Female
37
Figure 3. Age Distribution of Project Participants
Figure 4. Education Level of Project Participants
33%
29%
16%
22%
AGE DISTRIBUTION OF PARTICIPANTS
18-29 30-39 40-49 >49
9%
29%
40%
22%
HIGHEST EDUCATION OF PROJECT PARTICIPANTS
Completed High School Some College Undergraduate Degree Graduate Degree
38
Figure 5. Race Distribution of Project Participants
Figure 6. Project Participants in Healthcare vs. Non-Healthcare Job Role
16%
71%
4%
7% 2%
RACE DISTRIBUTION OF PROJECT PARTICIPANTS
Hispanic/Latino White African American Asian Other
11%
89%
HEALTHCARE WORKER VS. NON-HEALTHCARE WORKER
Healthcare worker Non-healthcare worker

39
Participant Health Knowledge
The first objective of this project was to determine if an online health educational
program would increase the health knowledge of participants. The paired sample t-test
was utilized to compare the pre-test and post-test scores from the Health Knowledge
Assessment Questionnaire. The data was of a normal distribution. Following data
analysis, it was noted that there was a statistically significant increase from mean pre-test
score (M=13.31, SD=4.07) to post-test score (M=15.36, SD=4.73) following the
intervention, t(44)=-5.288, 1-tailed p=<0.001 (Table 4).
The project investigator chose to regard a score of greater than or equal to 70% as
“knowledgeable” on the Health Knowledge Assessment Questionnaire and had set a goal
of an increase of 10-20% between pre- and post-test scores. The average pre-test score
was equal to 53% with the average post-test score equal to 61%. Neither average score
reached the “knowledgeable” threshold. A total of seven people scored 70% or greater
on the pre-test while a total of 15 scored 70% or greater on the Health Knowledge
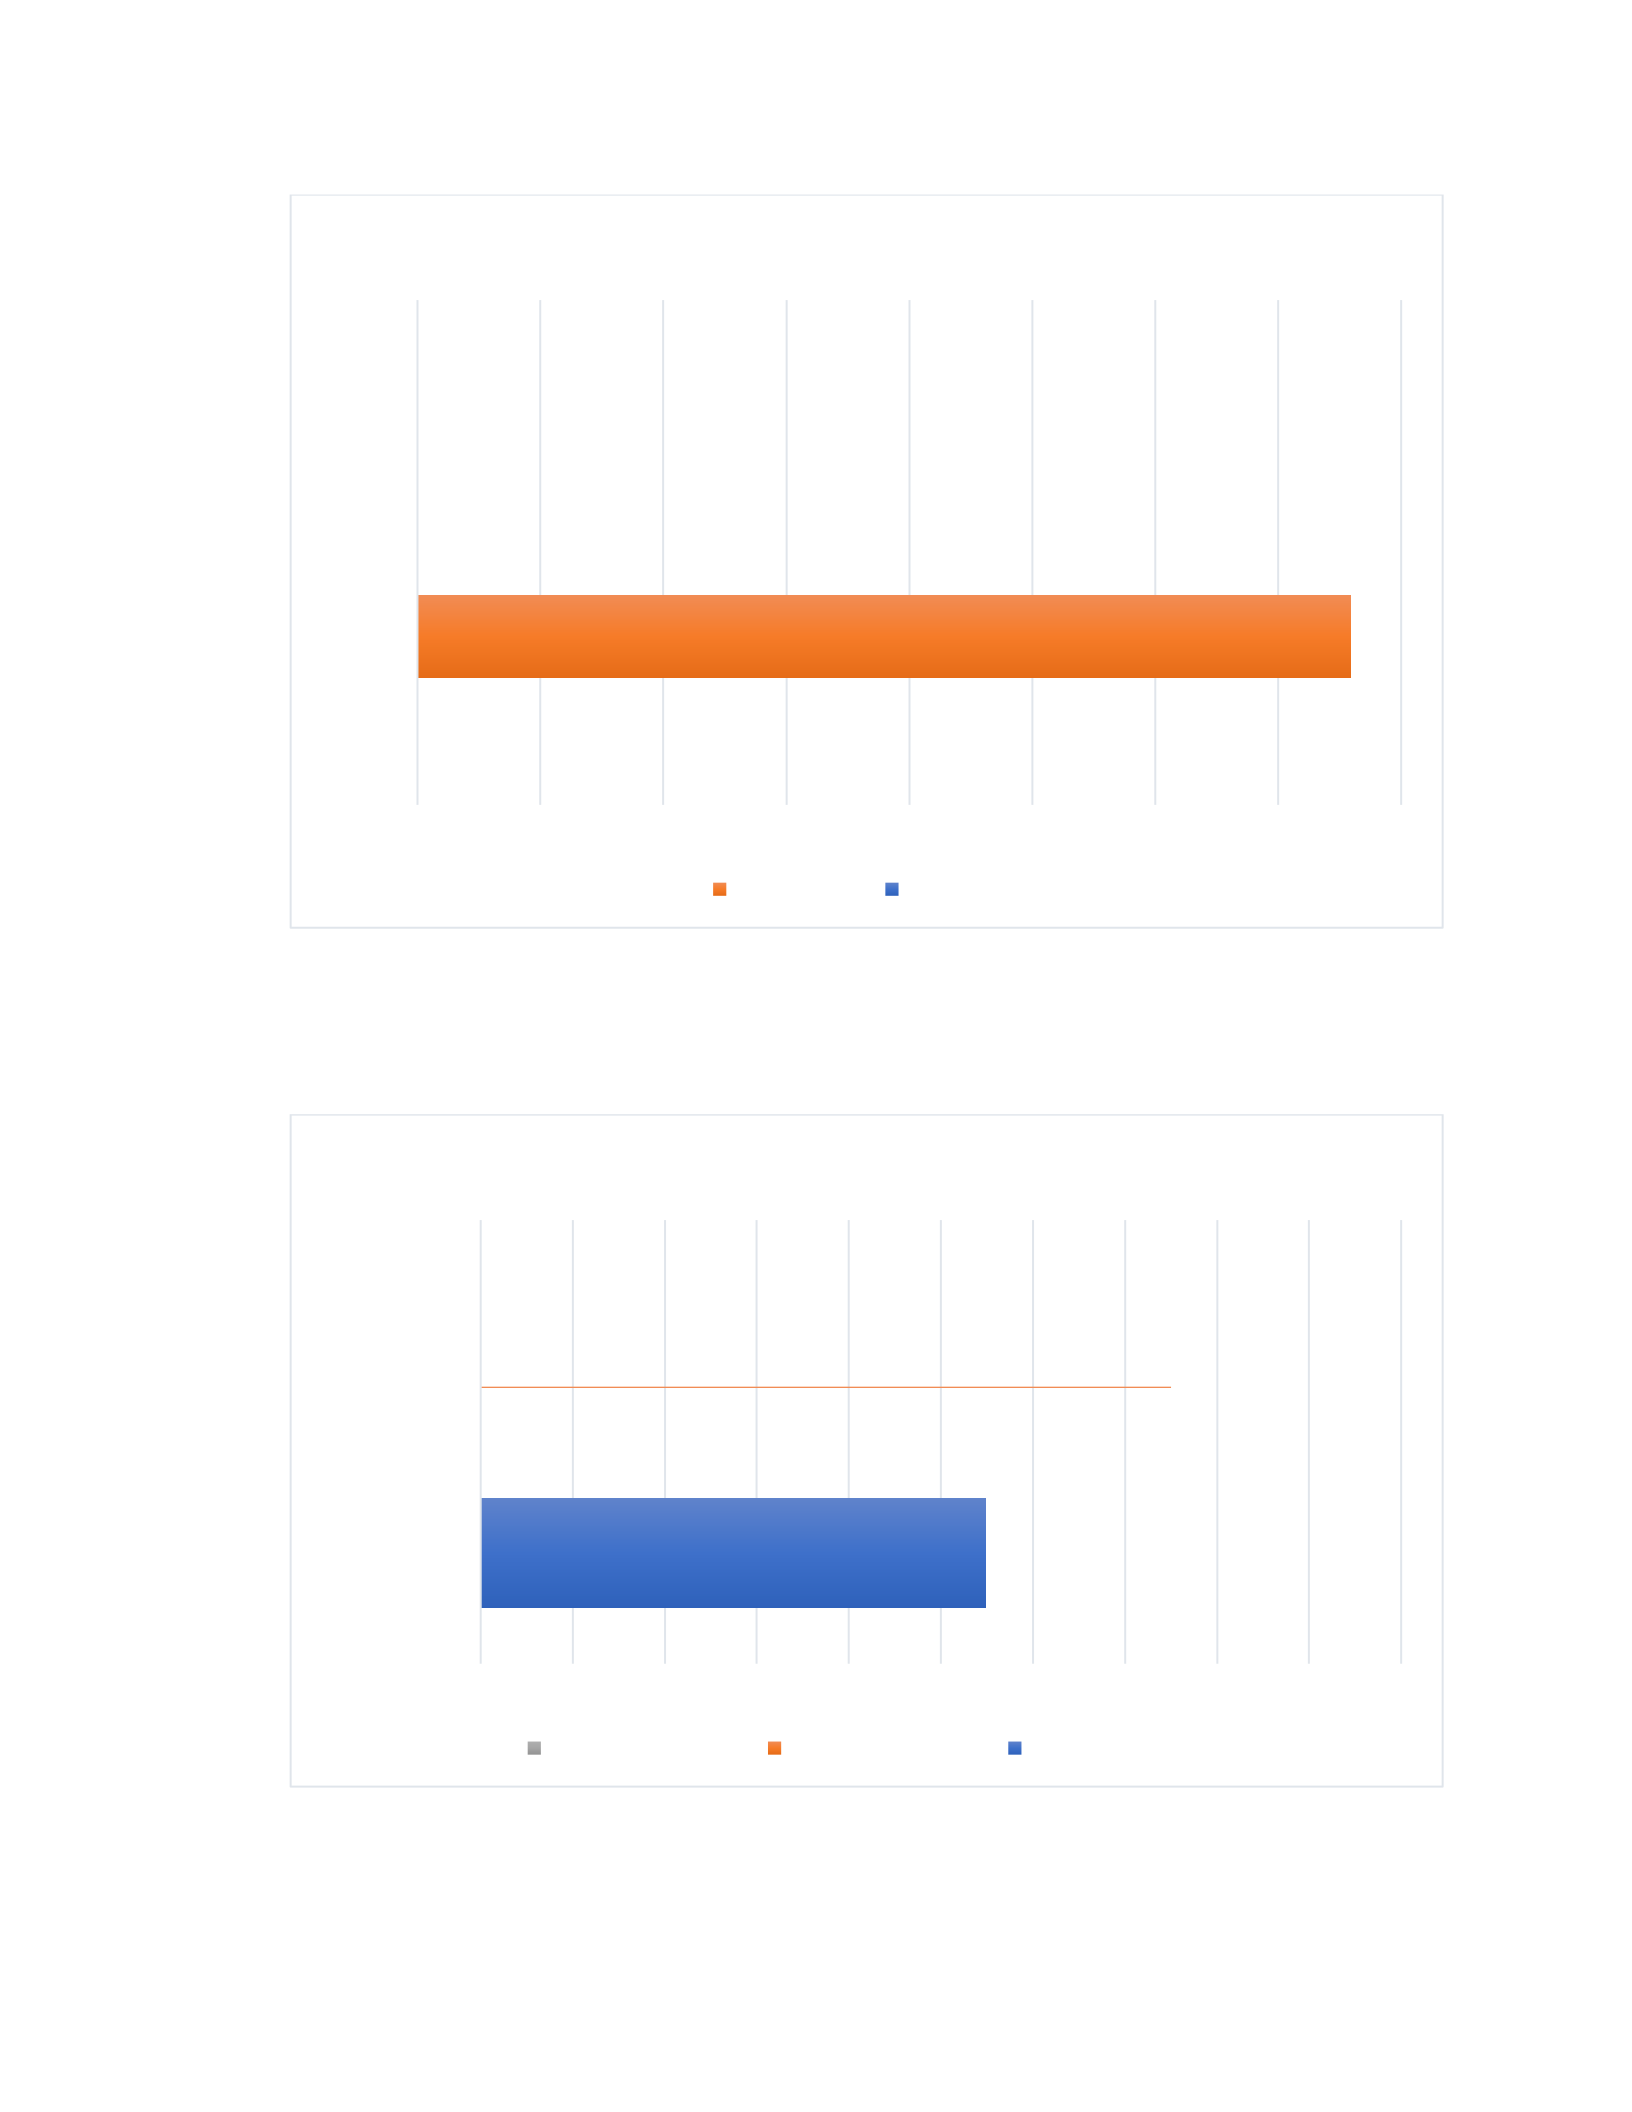
Assessment Questionnaire post-test (Figure 7). Although on average participants were
not considered “knowledgeable” regarding health knowledge, a total of eight people
crossed the threshold to “knowledgeable” following the intervention. On average, there
was an 8% increase in health knowledge which also did not meet the project
investigator’s goal. When the scores were further assessed individually, 11 people either
had the same score or a decreased score following the intervention, 15 people had an
increase in their score by less than 10% and 19 people had an increase in their score by
10% or greater (Figure 8).
40
Figure 7. Health Knowledge Scores <70% vs. >70% Pre-Test/Post-Test
Figure 8. Change in Health Knowledge Scores Post-Intervention
7
15
38
30
0 5 10 15 20 25 30 35 40
Pre-test
Post-test
Pre/Post-Test Scores </>70%
Scored <70% Scored >70%
11
15
19
0 2 4 6 8 10 12 14 16 18 20
Post-Test Score
Difference in Post-Test Scores
Increased by >10% Increased by <10% Same or Decreased

41
Association Between Demographics and Test Scores
The independent t-test was utilized to compare the mean pre-test and post-test
scores between male and female participants. There was a significant difference noted
between the mean scores of males (M=10.92, SD=3.53) and females (M=14.18, SD=3.95)
on the Health Knowledge Assessment Questionnaire. This difference was noted even
prior to the intervention, t(43)=-2.519, 1-tailed p=0.008; however, following the
intervention, the difference between the scores of males (M=12.25, SD=4.90) and females
(M=16.48, SD=4.19) was even more significant, t(43)=-2.865, 1-tailed p=0.003 (Table 6).
Females had higher means scores than males both pre- and post-intervention with means
scores of 14.18 and 16.48 respectively. Following the intervention, the means score in the
female group increased by 9%. Males scored an average of 10.92 on the pre-test and
12.25 on the post-test, accounting to an average increase of 5% on the post-test following
the intervention (Table 6).
There was not a statistically significant difference between the mean scores of
males and females on the General Self-Efficacy Scale either pre- or post-intervention.
Males, on average, scored slightly higher than females on the General Self-Efficacy
Scale. Both groups maintained almost identical mean scores pre-test and post-test.
Participants were grouped into four age categories for analysis to compare mean
pre-test and post-test scores for the Health Knowledge Assessment Questionnaire
utilizing ANOVA: ages 19-29, ages 30-39, ages 40-49, and age 50 or greater. When
comparing the mean pre-test scores of all four age groups before the intervention, there
was noted to be a statistically significant difference between these groups (19-29:
M=11.93, SD=3.00; 30-39: M=10.86, SD=2.77; 40-49: M=16.14, SD=3.45; 50 or greater:

42
M=16.70, SD=4.22) with a test statistic of F(3,41)=8.612, 1-tailed p=<0.001 (Table 6).
There continued to be a statistically significant difference between the four groups (19-
29: M=13.43, SD=4.11; 30-39: M=12.79, SD=3.93; 40-49: M=19.57, SD=4.43; 50 or
greater: M=18.70, SD=2.71) when comparing the mean post-test scores following the
intervention with a test statistic of F(3,41)=8.620, 1-tailed p=<0.001 (Table 6).
Post Hoc test using Scheffe criterion showed that the health knowledge score
prior to the intervention for age group 50 or greater (M=16.70, SD=4.22) was
significantly higher than the health knowledge score for age group 19-29 (M=11.93,
SD=3.00), p=0.007 or the health knowledge score for age group 30-39 (M=10.86,
SD=2.77), p=0.001. Also, the pre-intervention health knowledge score for age group 40-
49 (M=16.14, SD=3.45) was significantly higher than health knowledge score for age
group 30-39 (M=10.86, SD=2.77), p=0.007 (Table 8). The difference between mean test
scores became less significant post-intervention when comparing the health knowledge
score of age group 50 or greater (18.70 ± 2.71) with the health knowledge score for age
group 30-39 (M=12.79, SD=3.93), p=0.004 or the health knowledge score for age group
19-29 (M=13.43, SD=4.11), p=0.010. The difference between scores became more
significant when comparing the health knowledge score of age group 40-49 (M=19.57,
SD=4.43) with the health knowledge score from age groups 30-39 (M=12.79, SD=3.93),
p=0.003 and 19-29 (M=13.43, SD=4.11) p=0.007 (Table 8). The highest pre-test mean
score was noted in the 50 or greater age group (M=16.70, SD=4.22) while the highest
post-test mean score was noted in the 40-49 age group (M=19.57, SD=4.43). There was
an increase in each age group’s means scores post-intervention, however, the most

43
significant increase was noted in the 40-49 age group with an average increase of 3.5
points or 14% (Table 8).
Using the same age groups, mean General Self-Efficacy Scale pre-test and post-
test scores were compared between groups utilizing ANOVA. There was no significant
difference found between age groups when comparing scores either pre-test or post-test
(Table 7).
Upon recoding data for analysis by race and education, the data was found to not
be of a normal distribution; therefore, the Kruskal-Wallis test was utilized instead of
ANOVA to compare mean scores between education levels and the Mann-Whitney U test
was utilized instead of the independent t-test to compare median scores between white
and other races on the Health Knowledge Assessment Questionnaire scores. When
comparing median pre-test and post-test scores, there was no significant difference noted
between groups when comparing the median score of white participants to those of other
races or when comparing median scores between those with some college, an
undergraduate degree or a graduate degree either pre-test or post-test (Table 6).
Participant Self-Efficacy
The last objective was to determine whether online health education led to an
increase in self-efficacy. The paired samples t-test was utilized to compare pre-test and
post-test results from the General Self-Efficacy Scale. There was no significant
difference between pre-test and post-test self-efficacy scores, t(44)=-0.074, 1-tailed
p=0.471 (Table 4). The scores on the General Self-Efficacy Scale pre-test and post-test
were almost identical.

44
Table 4
Health Knowledge/Self-Efficacy Pre/Post-Test Results
Pre-Test
Post-Test
M ± SD
M ± SD
Statistics
1-tailed p-
value
Health
Knowledge
Assessment
Questionnaire
13.31 ± 4.07
15.36 ± 4.73
t(44)=-5.288
<0.001*
General Self-
Efficacy Scale
31.11 ± 4.06
31.16 ± 3.36
t(44)=-0.074
0.471
*p-value significant
Table 5
Demographics of Study Participants
Characteristics
n
(%)
M (SD)
Gender
Male
12
(26.7)
Female
33
(73.3)
Race
Hispanic/Latino
7
(15.6)
White
32
(71.1)
African American
2
(4.4)
Asian
3
(6.7)
Other
1
(2.2)
Healthcare Worker
Yes
5
(11.1)
No
40
(88.9)
Education
Less than high school
0
(0)
Completed high school
4
(8.9)
Some college
13
(28.9)
Undergraduate degree
18
(40.0)
Graduate degree
10
(22.2)
Age
45
38.04 ± 13.91

45
Table 6
Health Knowledge Assessment Questionnaire Scores According to Demographics
Characteristics
n
Pre-Test
Score
Statistics
Post-Test
Score
Statistics
M ± SD
M ± SD
Gender
Male
12
10.92 ± 3.53
t(43) = -2.519,
p=0.008*
12.25 ± 4.90
t(43) = -2.865,
p=0.003*
Female
33
14.18 ± 3.95
16.48 ± 4.19
Age
19-29
14
11.93 ± 3.00
F(3,41)=8.612,
p=<0.001*
13.43 ± 4.11
F(3,41)=8.620,
p=<0.001*
30-39
14
10.86 ± 2.77
12.79 ± 3.93
40-49
7
16.14 ± 3.45
19.57 ± 4.43
50 or greater
10
16.70 ± 4.22
18.70 ± 2.71
Mdn (Range)
Mdn (Range)
Race
White
32
13.00 (16)
U = 220.50,
p=0.377
15.50 (19)
U = 231.50,
p=0.276
Other
13
13.00 (12)
16.00 (12)
Education
Some College
13
14.00 (13)
H = 4.320,
p=0.058
16.00 (13)
H = 4.225,
p=0.061
Undergraduate
18
10.00 (13)
11.00 (19)
Graduate
10
13.00 (10)
16.50 (9)
*1-tailed p-value significant
Table 7
General Self-Efficacy Scale Scores According to Demographics
Characteristics
n
Pre-Test
Score
Statistics
Post-Test
Score
Statistics
M ± SD
M ± SD
Gender
Male
12
31.83 ± 2.86
t(43) = 0.717,
p=0.239
31.83 ± 1.47
t(43) = 1.174,
p=0.124
Female
33
30.85 ± 4.42
30.91 ± 3.81
Age
19-29
14
31.14 ± 3.88
F(3,41)=1.319
p=0.109
31.50 ± 2.71
F(3,41)=2.162
p=0.054
30-39
14
32.57 ± 2.90
32.57 ± 2.10
40-49
7
30.71 ± 5.31
30.14 ± 4.14
50 or greater
10
29.30 ± 4.55
29.40 ± 4.38

46
Table 8
Health Knowledge Assessment Questionnaire Scores According to Age-Group
Characteristics
n
Pre-Test
Score
p-value
Post-Test
Score
p-value
M ± SD
M ± SD
Comparison 1
19-29
14
11.93 ± 3.00
0.432
13.43 ± 4.11
0.489
30-39
14
10.86 ± 2.77
12.79 ± 3.93
Comparison 2
30-39
14
10.86 ± 2.77
0.007*
12.79 ± 3.93
0.003*
40-49
7
16.14 ± 3.45
19.57 ± 4.43
Comparison 3
30-39
14
10.86 ± 2.77
0.001*
12.79 ± 3.93
0.004*
50 or
greater
10
16.70 ± 4.22
18.70 ± 2.71
Comparison 4
19-29
14
11.93 ± 3.00
0.035*
13.43 ± 4.11
0.007*
40-49
7
16.14 ± 3.45
19.57 ± 4.43
Comparison 5
19-29
14
11.93 ± 3.00
0.007*
13.43 ± 4.11
0.010*
50 or
greater
10
16.70 ± 4.22
18.70 ± 2.71
Comparison 6
40-49
7
16.14 ± 3.45
0.495
19.57 ± 4.43
0.488
50 or
greater
10
16.70 ± 4.22
18.70 ± 2.71
*1-tailed p-value significant

47
CHAPTER 5
DISCUSSION
The main objective of this project was to determine if online health education
during a pandemic would result in an increase in health knowledge and an increase in
self-efficacy. Participant demographics were analyzed as well as the relationship of the
results to the project objectives and theoretical framework. Additionally, the project
strengths, limitations, implications for future research and practice, and how this project
related to the Doctor of Nursing Practice (DNP) Essentials as defined by the American
Association of Colleges of Nursing (AACN).
Participant Demographics
The smaller sample size made it difficult to analyze the data according to
demographics and limited the amount of variety seen within the demographic categories.
Although there was seemingly a lack of variety within the race category with 71% of
participants being white, 16% being Hispanic or Latino, 7% being Asian, 4% being
African American and 2% being classified as other, these percentages are similar to the
race demographics seen in Lincoln, CA and the surrounding cities (Table 9). The target
population of this project was Lincoln, CA and the cities surrounding it. The largest
cities included in Facebook Targeted Advertising included the cities of Lincoln, Rocklin,
and Auburn, CA. In each of these cities, white was the predominant race followed by
Hispanic (United States Census Bureau, 2019).

48
There was under-representation of male participants as the United States Census
Bureau reported approximately 50% of the population being female versus male in each
of the three aforementioned cities (2019). The United States Census Bureau only
reported educational statistics for high school or greater and undergraduate degree or
greater. For each of the three aforementioned cities, at least 92% of the population
finished high school and between 34-44% of the population had at least a bachelor’s
degree. All participants in this study reported at least finishing high school. Sixty-two
percent reported having an undergraduate degree or higher, however, it was difficult to
compare this to the education statistics from the United States Census Bureau since this
percentage also included those with an associate’s degree.
Table 9
Race Distribution in Lincoln, Rocklin, and Auburn, CA
Lincoln, CA
Rocklin, CA
Auburn, CA
White
68.2%
70.4%
83.8%
Hispanic/Latino
20.5%
13.1%
10.3%
African American
1.8%
2.1%
0.2%
Asian
6.3%
9.5%
2.0%
Note. Demographics for cities according to the United States Census Bureau, 2019.

49
Relationship of Results to Project Objectives
There were three objectives for this project:
1. To evaluate the effect of online health education on the health knowledge of the
community during a pandemic utilizing a health questionnaire pre-test and post-
test.
2. To explore the association between demographic factors and community health
knowledge.
3. To determine if online health education leads to increased self-efficacy utilizing
the General Self-Efficacy Scale as a pre-test and post-test.
Health Knowledge
Data from this research project demonstrated that there was a statistically
significant increase in health knowledge as measured by the Health Knowledge
Assessment Questionnaire pre-test and post-test. The average pre-test score on the
Health Knowledge Assessment Questionnaire was only 53% with an increase of eight
percentage points to 61% post-test. Although this fell short of the project investigator’s
goal of at least a 10% increase from pre-test to post-test score, almost half of participants
had an increase of at least 10% in their scores (Figure 8). This is significant because
research from the H1N1 pandemic of 2009 demonstrated that those who had access to a
greater amount of health education resources were more likely to participate and comply
with infection control measures (Wong & Sam, 2010; Van der Weerd et al., 2011). As
many people began growing weary of infection control measures such as mask wearing
and social distancing while the pandemic was still running rampant, increased health

50
education strategies was one strategy that could be utilized in order to increase
compliance with preventative measures.
As the focus shifted primarily to COVID-19, many routine health practices also
began to lose their role in people’s lives. Physical inactivity and sedentary behavior have
long been viewed as an ever-increasing public health risk, a pandemic in their own sense.
In the early phases of the COVID-19 response, research began to emerge warning of
potential long-lasting health concerns as a result of efforts to slow the spread of COVID-
19. Many opportunities for physical activity were thwarted as gyms and parks were
closed. People were starting to live more sedentary lives as they went into isolation and
stayed home the majority of the time. This was another side to the pandemic with
ramifications that won’t be fully understood for years into the future (Hall et al., 2020).
A previous study linked social isolation with unhealthy lifestyle practices relating to diet
and exercise in families with adolescent children (Thompson et al., 2019). Poor mental
health has long been understood to be exacerbated by social isolation (Hall et al., 2020).
Studies like these demonstrated that it was important to focus on routine public health
principles such as physical activity, healthy diet practices, and healthy social associations
even in the midst of a pandemic.
The Renew: Better Me, Better We program didn’t simply focus on narrowly
educating people regarding COVID-19 principles and practices. Instead, it focused on a
wide variety of topics that had a relation to COVID-19, but also affected lives in many
different areas. These topics included the importance of maintaining an active routine
and healthy diet even in the midst of social distancing and a pandemic. The series also
addressed the importance of maintaining social connections while still abiding by social

51
distancing practices. Like many previous pandemics, the COVID-19 pandemic
eventually will be a topic of the past, but the long-lasting health effects that resulted from
unhealthy lifestyle practices adopted because of the pandemic have the potential to
influence health well into the future. Because of this, interventions such as the Renew:
Better Me, Better We program that addressed a wide variety of lifestyle topics relevant to
the current times potentially were invaluable when it came to avoiding future public
health crises linked to unhealthy lifestyle practices associated with pandemic living.
Health Knowledge and Demographics
Because of the small sample size, it was difficult to make all of the demographical
comparisons desired by the project investigator. Some comparisons were able to be made
including between genders, age groups, and educational groups. Prior to the intervention,
there was a statistically significant difference between the health knowledge of males and
females. Females scored significantly higher than males on the Health Knowledge
Assessment Questionnaire pre-intervention. This trend continued post-intervention.
Post-test scores in the female group also increased more than the scores in the male group
(9% vs. 5% respectively). There was also greater representation in the female group.
Studies have demonstrated that females were more likely than males to be
interested in and engage in preventative health programs (Smith et al., 2018).
Additionally, women were more likely to utilize the internet to engage in education
regarding health-related topics (Smail-Crevier et al., 2019). Because of this, online
health educational interventions may be more attractive to females. Programs such as the
Renew: Better Me, Better We may have attracted more female participants because they
are already generally more interested in health topics than are males. Additionally, this

52
pointed out an area of improvement in that perhaps online health education could be
modified to better meet the needs of male participants in the future.
When mean scores of participants were compared based on race and education
level, there wasn’t a significant difference noted. As previously mentioned, the majority
of participants were white. This, along with the small sample size, made it impossible to
compare scores among each race group and required recoding of the race categories to
compare white with all other race groups. Similarly, there were only enough participants
in the “some college,” “undergraduate degree,” and “graduate degree” categories to
compare with each other.
Self-Efficacy
According to the authors of the General Self-Efficacy Scale, the purpose of the
tool is not to determine whether a person has high or low self-efficacy, therefore, there is
no pre-identified score cut-off to identify if participants have adequate self-efficacy. The
General Self-Efficacy Scale has been utilized in several large-scale studies in multiple
countries. In the United States, the average score was noted to be 29.48 in the adult
population with equal distributions of male and female (Schwarzer, 2014). The average
General Self-Efficacy Scale pre-test and post-test scores in this study were 31.11 and
31.16 respectively. Comparing these results with the average American adult’s scores,
participants in this study had slightly higher scores than the average American adult.
Relationship of Results to Theoretical Framework
The Health Belief Model has been utilized to guide many public health initiatives
in the past. It has sought to explain the health decisions and practices of human beings
based on the strength of their desire to avoid an illness or health threat compared to the

53
strength of their belief that engaging in certain behaviors would help avoid illness or help
them get well (Janz & Becker, 1984). A person’s perceived threat was defined as a
combination of their perceived susceptibility and perceived severity. The likelihood of a
changed behavior was also defined by the difference between a person’s perceived
benefits and perceived barriers of an action. Cues to action were the portion of the model
that drives an individual towards change. A person’s level of self-efficacy also was a
predictor of their likelihood to adopt new heath practices. A person’s demographics,
background and previous knowledge all effected their perception of health and illness as
well as their self-efficacy and likelihood to adopt new health practices (Janz & Becker,
1984).
The Health Belief Model was employed to help develop, shape and mold the
Renew: Better Me, Better We intervention. The intervention served as a “cue to action”
in the midst of a time of uncertainty and change. The Renew: Better Me, Better We
intervention communicated the severity of the COVID-19 pandemic as well as the
susceptibility of each individual to the disease. By incorporating simple and doable
lifestyle and behavioral modifications, the perceived barriers to change were minimized
and perceived benefits were highlighted. The goals of the project investigator were to
promote an increase in both health knowledge and self-efficacy. The design of the
intervention, having utilized the Health Belief Model as a guide, was successful in
increasing the health knowledge of individuals. According to the Health Belief Model, a
person’s health knowledge had a direct effect on their perceived barriers and perceived
expectations related to health practices (Janz & Becker, 1984). As an individual’s health
knowledge increased, their perceived benefits of engaging in a health promoting behavior

54
increased and perceived barriers decreased. This project was beneficial in that by
increasing the health knowledge of a community, the result of that increased knowledge
should be a willingness to engage in health promoting behaviors.
Without adequate self-efficacy, or the belief that one can accomplish what she
sets out to do, a person is unlikely to be successful. The goal of increasing self-efficacy
through this intervention was aimed to increase the chances that the participants would
engage in becoming healthier themselves. There wasn’t a significant increase in self-
efficacy, however, the individuals involved in the study already scored higher on the
General Self-Efficacy Scale than the average adult in the United States. In previous
studies that utilized the General Self-Efficacy Scale, the average score for the adult in the
United States was 29.5 (Schwarzer, 2014). Those who participated the research project
already had scores slightly higher than this on the pre-test.
Project Strengths
One significant strength of this project was the fact that it sought to fill a gap in
literature regarding education of the community during times of pandemic. There were
very few studies available regarding this topic. The study was performed in the midst of
the pandemic and utilized an approach that would be easy to duplicate and utilize in the
future during periods of pandemic.
Project Limitations
Significant improvements were noted in the health knowledge of participants
despite several limitations of this study. Two limitations were a smaller sample size and
utilizing convenience sampling. The smaller sample size limited the analyses that could
be performed especially for objective two due to some of the demographic categories

55
being missing or not having enough participants to accurately perform data analysis.
Lack of a control group and some data not being of a normal distribution were also
limitations of this study.
Implications for Future Research
Should this study be duplicated in the future, a larger sample size, employing a
random sampling method, and including a control group would be helpful for reducing
bias and making the results more generalizable. A larger sample size would allow for
more data points and more accurate analysis between demographical groups.
Implications for Future Practice
Periods of pandemic have existed throughout history. With each pandemic, there
have been public health initiatives aimed to control the spread of the disease. During a
time when technology was accessible to most individuals, it was an effective means for
healthcare providers to educate the public with accurate health information. Interventions
such as the Renew: Better Me, Better We program could also be utilized to dispel harmful
information that tends to circulate among the public during times of pandemic such as the
drinking of bleach that was promoted by some as a means to avoid COVID-19 during the
pandemic. Online health education could be utilized even during times of social
distancing and could also be an effective means of calming people’s fears during times of
uncertainty.
Dissemination
A trifold was developed by the project investigator detailing a brief description
and outline of the project and the results. This trifold was emailed to the mayor and
council members of the largest cities that were targeted for recruitment: Lincoln, Rocklin,

56
and Auburn, CA. In the email, the project investigator offered for the community leaders
to contact her if they were interested in obtaining more information about the project or
would like the project investigator to make a presentation regarding the project at a future
meeting. This same trifold was also provided the leaders at the Lincoln Amazing Grace
Seventh-Day Adventist Church. The project investigator also gave a short presentation to
the church in which a summary of the project and its results were reviewed.
Mastery of DNP Essentials
Essential I: Scientific Underpinnings for Practice
Essential I: Scientific Underpinnings for Practice was what encouraged the
nursing profession to close the gap between clinical practice and theory. Doctorate
prepared nurses should have been prepared to examine and understand both nursing-
based science and theory as well as science and theory from other professions in order to
translate the principles to practice to improve the whole person (AACN, 2006). This
project utilized a scientific theory, the Health Belief Model, along with an evidence-based
intervention, education, to fill a research and practice gap involving education of the
community during the COVID-19 pandemic.
Essential II: Organizational and Systems Leadership
Essential II: Organizational and Systems Leadership for Quality Improvement
and Systems Thinking involved the process of the advanced practice nurse constantly
being aware of the current patient, community and organizational needs. The nurse,
through her scientific education, was equipped with the ability to develop new care
models that are adapted to the specific healthcare needs of the targeted patient group
(AACN, 2006).

57
The project investigator noted a community need for accurate health education as
people from her church and in the community started asking for information regarding
COVID-19 and poor health practices began being recommended such as ingesting,
inhaling or cleansing the skin with antibacterial cleaning products. During the time of
COVID-19, group gatherings were completely eliminated for a period of time in
California as well as many other states. Hospitals were seeing far fewer patients than
usual and primary care offices closed their doors to inpatient visits for a period of time.
Not having access to healthcare professionals to answer questions and calm fears left a
population vulnerable to fear and to inaccurate health opinions from unqualified
individuals. This project was adapted to fill a need during a time when community
education from healthcare professionals was crucial.
Essential III: Clinical Scholarship and Analytical Methods
Essential III: Clinical Scholarship and Analytical Methods for Evidence-Based
Practice described the difference between a DNP and a PhD in nursing. The DNP-
prepared nurse combines clinical experience with the knowledge of scientific based
research and theories which is then translated into nursing practice. The DNP is the
healthcare provider that “bridges the gap” between science and practice, who translates
science into practice (AACN, 2006). The project investigator was able to utilize her
clinical experience as an acute care nurse to identify healthcare needs and then drew upon
her scientific knowledge of research and theory in order to have met those needs.
This project combined the clinical experience of the project investigator in caring
for acutely ill patients with COVID-19 with her knowledge of scientific research
regarding the pathophysiology and risk factors for the disease to create an online

58
educational series of videos that allowed the community members accurate education and
information. In the midst of fear, uncertainty and a barrage of health information from a
variety of unqualified sources, this series provided a voice of accuracy and reason and
disseminated accurate health information that provided participants the tools needed to
feel empowered.
Essential IV: Information Systems/Technology
Essential IV: Information Systems/Technology and Patient Care Technology for
the Improvement and Transformation of Health Care is provided to ensure that the
doctorate prepared nurse has an adequate knowledge of technology and information
systems, being able to incorporate them into evidence-based care to improve patient
outcomes and lead the practice in new, innovative methods (AACN, 2006). This project
utilized multiple avenues of technology through the internet. One of the primary avenues
of recruitment was through Facebook Targeted Advertising to the selected community
areas. Participants then accessed the consent form and pre-test on the SurveyMonkey
website. The project manager and her team member, Anil Kanda, recorded the health
videos on the computer utilizing both Zoom and iMovie. The videos were then uploaded
to the Panopto hosting site with a link specific to each email address then provided to
each participant. Utilizing Panopto allowed the project investigator to ensure that the
participants were each watching the majority of each health video. Lastly, the post-test
was also taken through SurveyMonkey.
Essential VI: Interprofessional Collaboration
Interprofessional collaboration is an essential skill that is present at the very core
of nursing. In fact, any member of a healthcare team must be skilled in the art of

59
interprofessional collaboration in order to provide safe care in the complex medical
environment (AACN, 2006). Essential VI: Interprofessional Collaboration for
Improving Patient and Population Outcomes was met by the project investigator during
this project as she constantly was collaborating with her team, the Lincoln Amazing
Grace Seventh-Day Adventist Church, and Andrews University’s information technology
department. The project investigator utilized evidence-based research in the development
of an educational health curriculum relevant to COVID-19 targeting the city of Lincoln,
CA and surrounding cities. Throughout this process, she depended on the expertise of
her teammates, which included a DNP and pediatric nurse practitioner, PhD prepared
nurse, a medical doctor and an individual with a master’s in public health, to provide
insight, direction, and critique of the curriculum and project. She worked in
collaboration with the Andrews University information technology department to activate
a Panopto account to host the health videos. Additionally, she collaborated with her team
and community members to develop the Health Knowledge Assessment Questionnaire.
Essential VII: Clinical Prevention and Population Health
Unhealthy lifestyle behaviors account for many chronic diseases seen in the
United States and other parts of the world. Cardiovascular disease is the leading cause of
death in the United States. It is believed that 33% of deaths from cardiovascular disease
could be avoided by making healthier lifestyle choices (Lanier et al., 2016). The CDC
(2014) reported that approximately 40% of annual deaths in the United States would
likely be preventable by lifestyle changes. As previously discussed, many of those who
are experiencing severe COVID-19 symptoms have pre-existing lifestyle diseases such as
obesity, heart disease, and diabetes (CDC, 2020d).

60
The project manager met Essential VII: Clinical Prevention and Population
Health for Improving the Nation’s Health by incorporating information and simple
strategies to engage in heathy lifestyle choices in the Renew: Better Me, Better We
curriculum. Participants were encouraged to make small lifestyle changes such as
adding different colored foods to the diet, aiming to eat a serving of beans every day,
aiming to spend 15 minutes in the sun and exercise for 30 minutes as many days as
possible, making an effort to connect with friends and family via the telephone and video
chat and creating a journal to write down things for which to be thankful. Although these
lifestyle changes likely came too late to make a significant difference in mortality and
morbidity rates during the COVID-19 pandemic, similar lifestyle changes have been
shown to improve quality of life in the short-term. Long-term benefits of a healthier
population could be demonstrated in future pandemics.
Essential VIII: Advanced Nursing Practice
Essential VIII: Advanced Nursing Practice describes the role of the advanced
practice nurse in her area of specialty. The DNP prepared advanced practice nurse has a
wide variety of clinical experience with a mastering of a specific, chosen area of
emphasis. The DNP education prepares a nurse to conduct complex patient assessment
while incorporating patient-centered and culturally sensitive interventions that are
evidence-based, develop therapeutic relationships with patients and colleagues, serve as a
mentor to other nurses, provide education and guidance to individuals as they navigate
through complex situations, and, finally, evaluate the policies and practices in place
(AACN, 2006).

61
The project investigator met this essential by developing a community-centered
curriculum to help guide residents through the COVID-19 pandemic with confidence.
Having also chosen a specialty in family practice nursing, the project investigator chose
presentation topics that were relevant to her specialty such as disease prevention and
health promotion.

