


1
CHAPTER 1
INTRODUCTION
The world now faces an unprecedented time where the senior population will
soon surpass that of children, thus leading to the majority of the population being old or
very old (Zarghami et al., 2018). According to the United Nations, the senior population
is the fastest-growing population in the world (Oliveira et al., 2018). In the United States,
there is a growing number of community-dwelling senior people who present with
increased risks of untoward health effects that come along with aging (Marcus-Varwijk et
al., 2019).
Background and Rationale
There is an increase in the number of seniors living alone (Ng et al., 2015). Living
alone is one of the noticeable factors that affect the well-being of seniors with evidence
that this population most frequently presents with increased risk for reduced hope,
depression, deconditioning, falls, injuries, infections, dehydration, and hypothermia (Yeh
& Lo, 2004). There is also an increased risk for high mortality because of a lack of social
connections and support in this population (Ng et al., 2015). There is an association
between living alone and decreased level of hope and quality of life (QOL) in the senior
population.
Quality of life is the term used to describe an individual’s health and it is an

2
essential external indicator that reflects the internal being. Quality of life is also perceived
as an essential health research outcome (Hayhurst et al., 2014). Even though QOL is
usually referred to as the reflection of an individual’s health, research findings show that
this indicator includes both health-related factors and non-health-related factors such as
family, friends, jobs, and circumstances of life (All et al., 2017). The QOL in the senior
population is a global issue and a twenty-first-century challenge. Several factors affect
QOL in seniors (Ahmed, 2020), and many research studies have been conducted to
evaluate this vital indicator in this population. Senior people who live alone experience a
higher degree of reduction in their QOL due to isolation, feelings of loneliness, pain,
depression, anxiety, powerlessness, and hopelessness. Loneliness is a multi-dimensional
and complex feeling which has a significant impact on the health and the well-being of
the senior population. Seniors are particularly vulnerable to this feeling because of their
fragility (Rocha-Vieira et al., 2019). Many research studies have been conducted to seek
the impact of loneliness on physical, emotional, and behavioral problems (Rokach, 2007).
Loneliness is a serious threat to seniors’ lives and their QOL (Rocha-Vieira et al., 2019).
Interventions to promote and increase the QOL are essential in reducing or eliminating
the challenges the senior population faces in the twenty-first century.
Hope is an inner source that can enrich life and improve the outlook on life.
Studies conducted to assess the level of hope and its effect on QOL show that there is a
strong connection between the levels of hope and coping with life events. People who
have a higher level of hope adjust to and manage life events effectively with acceptance
and normal ways of living (Chi, 2007). People identify different strategies to foster hope
and cope with life changes.

3
The literature review indicated that the utilization of non-pharmacological
interventions such as hope and affirmation had positive effects on the QOL Hope is at the
core of human psychology and is a powerful vital force linked to health (Stavarski, 2018;
Leontopoulou, 2020).
Healthcare professionals have an important role in enhancing hopefulness through
hope interventions. Hope can be offered through building relationships with patients and
families, being present, listening actively, giving attention to small improvements in care,
providing comfort, encouraging hope in their religious beliefs, and giving patients what
they needed (Stavarski, 2018).
Hope-fostering interventions and programs aim to promote overall well-being and
reduce psychopathology in a variety of populations and various settings such as
educational organizations, recreational centers, correctional institutions, and therapy and
counseling. Studies indicate that hope-fostering interventions enhance psychosocial
outcomes and reduce depression (Larsen et al., 2015; Leontopoulou, 2020).
Problem Statement
The senior population who lives alone faces many challenges that affect their
general well-being and overall QOL. Seniors who live alone are more vulnerable to
reduced hope and QOL due to a lack of access to the available resources (Haslbeck et al.,
2012). With this fastest-growing population, the world faces an increase in the health-
related challenges that come with this population. Declining hope and QOL in seniors
living alone pose a significant problem both to the healthcare industry and society. While
many pharmacological interventions to improve the level of depression and outlook
towards life have been used in practice, several non-pharmacological interventions that

4
are available as an alternative to pharmacological treatments have not been effectively
utilized to improve hope levels and QOL in this population.
According to Herth (2001), hope was seen as being vital in strengthening
physiological and psychological defenses (Herth, 2001). In nursing, medicine, and mental
health, an intervention to give or improve hope had been considered to be one of the
interventions. Health care professionals, through non-pharmacological interventions such
as touch, being present, listening, encouraging, and providing education, can reduce the
feeling of hopelessness and increase the level of hope leading to improved QOL (Binaei
et al., 2016). Hope reflected an individual perception of inward potential to overcome a
challenge. Due to this very nature of hope, hope intervention was considered as an
alternative to medication management in positively influencing the QOL (Stavarski,
2018).
Many senior people live alone with no support from their family or society. They
are depressed and without hope. Hope intervention has shown good effects on decreasing
depression and increasing s sense of hope in other populations (Salamanca-Balen et al.,
2021). However, not many studies have been done on the effects of hope intervention on
senior people who live alone. Hence, this study plans to evaluate the effects of Hope
Interventions on senior people who live alone through the Hope Intervention Program
(HIP).
Purpose Statements
The purpose of this project was to investigate the effects of a non-
pharmacological intervention, the hope intervention, on hope and the QOL of senior
people who lived alone.

5
PICOT Question
How does the implementation of an eight-week hope intervention in seniors 65
years and older who live alone affect their level of hope and quality of life compared to
those levels in seniors 65 years and older who live alone and do not receive the hope
intervention?
P – Seniors 65 years and older who live alone
I – Hope Intervention Program
C – Seniors 65 years and older who live alone and receive hope intervention and
those who do not receive hope intervention
O – Level of hope and QOL
T – After eight weeks of the hope intervention program

6
CHAPTER 2
LITERATURE REVIEW/CONCEPTUAL DEFINITIONS/
THEORETICAL FRAMEWORK
Literature Review
The purpose of the literature review was to examine previous research on the
effects of hope intervention on the level of hope and QOL and how that may affect senior
people who live alone. The literature review was completed by using the EBSCOhost
health search engine, which included other databases such as the Cumulative Index to
Nursing and Allied Health Literature (CINHAL), Google Scholar, PubMed, and
ProQuest. Studies were selected based on their relevance to the current study.
Keywords: Seniors, elderly individuals, loneliness, loneliness in older adults,
chronic diseases in older adults, well-being, quality of life in older adults, loneliness and
quality of life, hope, hope interventions, and hope interventions in seniors.
Hope
The word “hope” comes from Old English word “hopa” and translates to having
confidence in the future (Safri, 2016). Very few people are knowledgeable in the science
of hope (Gwinn & Hellman, 2019). Hope is seen as something aspiring, a positive
anticipation of the future, something good to look forward to. It is usually directed
towards the future and reflects personal will power (Safri, 2016; Van Dongen, 1998).

7
Hope is as old as humanity and vital for the existence of humanity. Hope
influences how a person thinks and acts. Hope not only shapes people’s behavior, but also
motivates them and enables them to keep going during times of distress, discouragement,
and disappointment. Hope creates new possibilities and fills people with strength,
courage, and happiness to move on in life with renewed energy (Safri, 2016). When
individuals have hope, they can change the course of their situation (Van Dongen, 1998).
Hope’s desire can be long-term and even a lifelong endeavor. Hope represents how
individuals perceive their ability to frame their goals, create strategies to meet those
goals, and sustain their motivation to implement those strategies (Chi, 2007; Snyder et
al., 2003). Hope can grow and thrive in the environment where a culture of hope is
valued.
Culture of Hope
Hope is recognized as a bridge between the impossible and the possible. Hope is
sometimes dramatic in harrowing and life-saving events, while at other times, it is seen in
the quiet activities of daily life. Martin Luther King, Jr. embraced hope as the foundation
of creating a hopeful world. He used to love to say that everything that is accomplished in
the world was accomplished by hope (Gwinn & Hellman, 2019). Once people understand
hope, they have the choice to believe in it and then put forth efforts to obtain it. Once
individuals achieve hope, then they can recruit others to develop a community of hope,
thus creating a culture of hope. There is a greater power in the collective culture of hope
than individual hope. Building a culture of hope has shown to support individuals with
purpose, pride, place, and optimism (Gibson & Barr, 2017; Gwinn & Hellman, 2019).
Where the culture of hope is not promoted, outcomes can be less than optimal and

8
leading to a negative outlook towards life and reduced QOL.
Hope, Illness, and Healing
Illness is a disease condition in which the body or mind is affected. Healing is an
act or process of restoring to health. Hope can play a vital role in healing and coping.
Medical professionals and researchers are increasingly seeing hope as a dynamic,
cognitive, emotional, and motivational process, as well as a way to cope with disease
conditions (Salamanca-Balen et al., 2021). Hope can help individuals cope with serious
and chronic threats to their physical and psychological well-being, leading to enhanced
QOL (Salamanca-Balen et al., 2021). While hopelessness has been linked to depression
and suicide, hope involves having confidence in and expectations of a brighter future in
the face of adverse circumstances (Gupta & Singh, 2020). In psychological and
psychiatric literature, hope is seen as a longing for the betterment of a hopeless outcome,
operationalizing it as a positive goal-related (future-oriented) motivational state and a
dispositional trait that signals a tendency to adopt a positive outlook (Gupta & Singh,
2020). It has further been established that hope can be measured as an essential
restorative factor in the field of healthcare and recovery (Lucas et al., 2019). Hope can
also be fostered through interventions in individuals facing adverse health conditions,
loneliness, and from living alone (Gupta & Singh, 2020).
Quality of Life
Within the arena of health care, QOL is viewed as multidimensional, and
encompassing physical, psychological, emotional, and social well-being. Quality of life is
a multifactor and a value-driven concept (Soósová, 2016). The most important aspects of

9
QOL in the elderly are autonomy, decision-making power, independence, self-sufficiency,
preservation of health and sensory abilities, absence of pain and illness, economic
security, connectedness with family and friends, and peace and happiness. Quality of life
in the elderly can be negatively influenced by many demanding factors related to the
aging process. The elderly faces a variety of challenges ranging from changes in health
status, identifying with new roles, adjusting to changing social support, and coping with
new restrictions in life posed by the aging process (Soósová, 2016).
Elderly people suffer from economic insecurity and loss of power as they age and
retire from their work, thus leading to reduced QOL. The QOL of the elderly has been a
global concern and is becoming increasingly important for research because of its effect
on public health (Wayadande & Prabhakar, 2020). Quality of life in the elderly is directly
associated with their perceived well-being; hence, it is essential to provide the elderly
with the opportunity to live a long quality life with an understanding that the aging
phenomenon is not only physical, but also a social element that affects how the elderly
feel, live, relate to their life, to other people in their lives, and to their environment (dos
Santos Gomes et al., 2020).
Quality of Life in Senior People Who Live Alone
Quality of life is impacted by living alone. Solitude is worst when people live
alone. They are more vulnerable to poverty, and deprivation becomes more probable the
longer they live alone. Many elderly individuals who live alone express feelings of
isolation and loneliness. Given that dining is primarily a social activity for most
individuals, some elderly persons who live alone do not make complete, well-balanced
meals (Davie-Smith et al., 2017). Eating habits especially tend to change over time

10
because chronic conditions may overpower the aged and even the strength to prepare a
meal for themselves is a great struggle. The lack of a balanced diet causes their health to
deteriorate. Again, the lifespan of older adults living alone declines each day of their
lives. This could be because of illness due to underlying issues (O'Súilleabháin et al.,
2019).
Factors Affecting the QOL in Senior People
Aging is the progressive phenomenon of change in the physiological,
psychological, and social aspects of an individual. Aging is seen as a holistic concept
since it involves a broad range of issues (Ahmed, 2020). According to the World Health
Organization, those who are entering into their senior life-cycle experience biological,
social, and psychological changes (Bahramnezhad et al., 2017).
In the United States, debilitating conditions such as heart disease, dementias, type
2 diabetes, arthritis, and cancer are the leading drivers of disability, deaths, and healthcare
expenditure. Studies indicate that seniors age 60 and older experience Alzheimer’s
disease and other dementias at a greater rate compared to other age groups, and the risk
for these conditions increases with age. Healthcare and long-term care expenses
associated with these conditions greatly increase the financial burden of healthcare in the
United States to the amount of $290 billion in 2019 (CDC, 2020).
Loneliness and Its Effects on QOL
Loneliness plays a vital part in the physical, psychological, and social
deconditioning of seniors who live alone. Human beings, generally speaking, are social
creatures who, in order to live successfully, need safe and secure social environments to

11
thrive (Hwang et al., 2020). Social connections that are satisfying are essential for both
mental and physical well-being. Having strained social relationships may contribute to
feelings of loneliness. People who participate in meaningful, valuable activities with
others have a better mood, live longer, and have a greater sense of purpose than those
who do not. According to research, these activities seem to aid in maintaining mental
well-being and may even enhance their cognitive performance. The perception of
loneliness as a worldwide human issue has existed since the beginning of humanity
(Hwang et al., 2020).
Isolation may result in various mental illnesses, including depression, sleep
difficulties, personality disorders, alcoholism, and Alzheimer's disease. There are also
numerous physical illnesses such as type 2 diabetes, autoimmune illnesses, osteoarthritis,
lupus, as well as cardiovascular problems such as heart disease, physiological aging, high
blood pressure (HTN), cancer, obesity, and poor health are all examples of chronic
conditions and impaired hearing as a result of smoking (Hwang et al., 2020). The effects
of loneliness on people’s emotional and physical health, if left untreated, may be very
detrimental. As a result, it is critical to act at the appropriate moment to avoid loneliness
and ensure that patients’ physical and emotional health is preserved.
Loneliness is primarily evident in senior people. Research shows that this could
be due to living alone, detachment from the tradition of origin, or neglect by close family
ties (Hwang et al., 2020). This causes the elderly not to participate fully in society.
Loneliness, especially in seniors, has been linked to an increased risk of anxiety, sadness,
cognitive decline, vascular dementia, and even mortality. Particularly vulnerable are
those who find themselves suddenly alone due to circumstances such as the death of a

12
spouse or partner, retirement, separation from friends or family, loss of mobility, or lack
of transportation. Physical effects like sleep deprivation, weight gain, weak immune
system, and poor heart health can be evident (Hwang et al., 2020).
Effects of COVID-19 and Isolation on Seniors
During the outbreak of Covid-19, social isolation became mandatory in most
places, especially for the elderly because they were most vulnerable to this virus.
Regardless of whether they were infected or not, the elderly, were restricted to their
homes. It had been suggested that the impacts of COVID solitude might be particularly
acute among older individuals in long-term care (LTC) amenities (Kasar et al., 2020). The
literature review indicates that residents’ feelings of loneliness, despair, abandonment,
and fear and their impact on neurobehavioral health contributed to the rise in the number
of deaths associated with the epidemic. Seniors’ physical and mental health was adversely
impacted by the social distance that occurred throughout the COVID-19 pandemic. As a
result, throughout the confinement period, a multi-component program that included
exercise and psychological techniques were highly suggested for this group of people
(Kasar et al., 2020).
Hope and Quality of Life
Important aspects of QOL include autonomy, decision-making, independence,
self-sufficiency, preservation of health and sensory abilities, absence of pain and illness,
economic security, connectedness with family and friends, and peace and happiness
(Soósová, 2016). Quality of life is one of the most important factors that affect the
disabled and elderly (Zareei Mahmoodabadi et al., 2019). Quality of life in the elderly

13
can be negatively affected by many demanding factors related to aging. Elderly
individuals face a variety of challenges ranging from changes in health status, adapting to
new roles, adjusting to changing social support, economic insecurity, and coping with
new restrictions posed by advanced age (Soósová, 2016).
Quality of life of the elderly has been a global concern and is becoming
increasingly important for research because of its effect on public health (Wayadande &
Prabhakar, 2020). Quality of life in the elderly is directly associated with their perceived
well-being; therefore, it is essential to provide the elderly with the opportunity to live
long, quality lives and the understanding that aging is not only physical, but also affects
how individuals feel, relate to their life, to other people, and their environments (dos
Santos Gomes et al., 2020). A perceived sense of wellbeing is essential and is strongly
related to improved QOL.
Researchers have long sought to understand the association between hope and
QOL. One study indicates that vitality is one of the important mechanisms accounted in
attaining hope and thus leading to improved QOL. Vitality reflects an individual’s
subjective experience of energy and activity. Vitality is associated with better physical
and psychological health in adults (Lucas et al., 2019). In order to evaluate vitality’s role
in mediating the relationship between dispositional hope and QOL, Lucas et al. (2019)
recruited a sample of 101 adults from a community-based primary care setting in the
United States. The sample included 72 women and 29 men, mostly Caucasian, from 18–
64 years of age. Lucas et al. (2019) assessed hope using the Hope Scale; previous
researchers identified positive relationships between the Hope Scale and personal control
and self-esteem measures, indicating validity for the scale. Lucas et al. (2019) found that

14
vitality fully mediated between hope and QOL, which included aspects of physical
health, psychological health, social relationships, and environment, confirming the fact
that vitality is a significant mechanism through which hope affected QOL in adults. The
results indicated the need for promoting environments that foster vitality to help activate
hope and promote QOL of adults.
Adult QOL can be negatively impacted by issues related to aging and disease. The
QOL of older adults includes social, psychological, physical, and spiritual factors.
Additional individual-level characteristics that affect well-being include activity,
productivity, income, social status, physical and mental health, longevity, cognitive
efficacy, strong relationships, and satisfaction in life (da Silva & Baptista, 2019). Lack of
purpose in life can lead to reduced QOL and to negative perceptions of life, which can
then lead to reduced hope and meaning in life (Binaei et al., 2016). Focusing on vitality
when caring for adult patients can help facilitate hope and lead to enhanced QOL
outcomes (Lucas et al., 2019). Hope as an inner force has been shown to strengthen and
uplift individuals’ spirits and allow them to look beyond current circumstances (Binaei et
al., 2016).
Researchers have also focused on medically oriented external factors in relation to
hope, such as chronic illnesses, health disparities, health insurance, and how they are
linked to QOL. Chronic illnesses can lead to impaired functional ability (Binaei et al.,
2016). Considering the health disparities related to insurance in the United States,
Wippold and Roncoroni (2020) conducted a study involving structural equation
modelling and 197 adults living with at least one ongoing comorbid ailment. They
examined the relationships between various chronic health issues, the two components of

15
hope related to agency and pathways, and the health-related QOL among the population.
Pathways and agency are two essential factors in achieving any desired goals. Pathways
are ways people identify that will aid them reach their goals. Agency reflects individuals’
perception of their ability and the drive to achieve their goals. In this study, the hope of
the individuals was tested using the State Hope Scale. They found that multiple
comorbidities, including heart disease, stroke, diabetes, and cancer negatively impacted
the high quality of life of the affected populations. The findings further indicated that
agency mediated the relationship significantly, resulting in positive outcomes (Wippold &
Roncoroni, 2020). Wippold and Roncoroni (2020) emphasized that it is important to
encourage individuals to take charge, have hope, and control their lives in order to
manage chronic health diseases and survive despite the difficulties. Gaining the
motivation to achieve their goals and control their health could enhance hope, even in the
face of long-term diseases and being uninsured or underinsured. An improved attitude of
readiness to attain goals along with hope can help enhance the QOL and health status
(Wippold & Roncoroni, 2020). In an earlier study, Binaei et al. (2016) also found that
severity of heart failure and an uncertain prognosis of this disease impact QOL
negatively; however, hope-promoting strategies were found to be beneficial in improving
this condition. Hope is dynamic and can empower individuals to reach the desired goal
(Chamodraka et al., 2017).
Researchers have also investigated the relationship between hope and QOL in
various types of patients. Alshraifeen et al. (2020) studied the correlation between hope
and QOL among hemodialysis (HD) patients in Jordan. The researchers contended that
hope was important for end-stage renal-disease patients. These individuals received HD

16
to manage the condition, and hope was thought to be closely related to QOL in this
population. The study involved a cross-sectional design, and 202 convenience patient
samples from six varying dialysis centers were included to evaluate the association
between hope and QOL. The World Health Organization QOL-BREF and the Herth Hope
Index (HHI) were used to measure QOL and hope, respectively. The researchers
identified moderate levels of hope with a viable mean, and participants showed low mean
scores for physical, domain-related QOL. The results revealed that the physical domain
might not be related to hope. However, the findings also revealed that the social and
psychological relationship aspects had improved hope levels related to the QOL. Overall,
study results indicated a positive correlation between the level of hope and QOL in
people receiving HD for end-stage renal disease (Alshraifeen et al., 2020). Patients
receiving HD to manage end-stage renal conditions needed assistance developing hope in
their environments. Alshraifeen et al.’s (2020) findings emphasized that introducing hope
and promoting care while serving HD patients in healthcare facilities could improve their
QOL. These patients often experienced considerable levels of stress since they had to
attend HD sessions for the rest of their lives and they required quality care to improve
their health outcomes. The results showed that understanding the association between
hope and QOL could help healthcare professionals improve the type and level of care
provided to their patients and their families. This information is essential in giving hope
when caring for HD patients in consideration of the expected positive outcomes in their
QOL (Alshraifeen et al., 2020).
Quality of life can also be critical in the decision-making process related to
medical conditions, their management, evaluating outcomes, and future interventions.

17
Shen et al. (2020) investigated the correlation between hope, self-efficacy, and social
support in 121 triple-negative breast cancer patients as they battled the condition. The
study included a cross-sectional design and patients at the breast cancer treatment center
in Tianjin Medical University Cancer Institute and Hospital, Tianjin, China. The
researchers used convenience sampling to bring participants on board. Participants were
above 18 years old, receiving post-surgery chemotherapy with no prior diagnosis of
cancer, and could communicate in Chinese (Shen et al., 2020). Shen et al. used the HHI
to measure hope, the General Self-Efficacy Scale (GSES) to measure self-efficacy, and
the Functional Assessment of Cancer Therapy Breast Cancer (FACT-B) to measure QOL.
Data were analyzed with independent sample t-tests, one-way Pearson correlation, and
multiple regression analysis (Shen et al., 2020). Shen et al. (2020) found that hope, self-
efficacy, and social support were strongly correlated with the QOL in breast cancer
survivors (P<0.001). Higher-income was shown to contribute to better QOL. The
multiple regression analysis of this study showed that hope, income, cancer stage, self-
efficacy, and social support were significant predictors of the patients’ QOL (P<0.001).
Hope, social support, self-efficacy, and income were observed as positive factors of QOL,
while the cancer stage was the negative predictor of the QOL (Shen et al., 2020). Hope, a
positive predictor of QOL, was an effective strategy that provided adaptive power to help
cancer patients overcome a difficult situation and achieve desired outcomes (Chi, 2007).
Shen et al.’s (2020) study highlights the need for intervention programs to support and
improve income, hope, self-efficacy, and social support for this patient population in
order to improve their QOL.
Understanding the needs of the elderly is crucial to caring for them

18
(Bahramnezhad et al., 2017). One of the domains of well-being involves the social aspect
of QOL. A supportive environment or a sense of community plays a vital part in
individuals recovering from an injury or assault (Bahramnezhad et al., 2017; Stevens et
al., 2019). Considering the challenges individuals endure in the disease recovery process,
Stevens et l. (2019) conducted a cross-sectional study using a sample of 229 individuals
from three Oxford houses, including democratic, self-running recovery homes, and the
largest network of self-recovery homes in the United States, to identify the role of hope
and community in supporting recovery. Stevens et al.’s (2019) study included a 55% male
and 44.5% female population with the mean age of 38.4 years from multiple ethnic
groups. Stevens et al. used Snyder’s State Hope Scale to measure hope, the Psychological
Sense of Community Scale to measure sense of community, and the World Health
Organization Quality of Life Assessment Brief Version to measure the QOL. Stevens et
al. (2019) assessed whether hope and sense of community predicted the QOL for
populations living in recovery homes, and the findings revealed that both hope and sense
of community were primary predictors of QOL, suggesting they can aid significantly in
the recovery process. However, age, race, and length of stay did not impact the QOL and
hope during recovery (Stevens et al., 2019). There is a strong relationship between all
aspects of social networks and QOL. While hopefulness is often conceptualized as an
individual-level factor, Stevens et al.’s (2019) findings emphasized that hope can
originate from a sense of community, and both factors can lead to improved QOL, thus
aiding in recovery. Stevens et al. (2019) recommended that hope and a sense of
community be encouraged to improve QOL and recovery in patients with challenging
conditions. Another study indicated that creating an environment to promote and improve

19
relationships among the elderly and other social networks of family, friends, and
neighbors has shown to lead to an improved QOL in the elderly (Bahramnezhad et al.,
2017). Based on the previous researches, the current study may indicate improvement in
the physical, emotional, and psychological aspects of QOL in the elderly through hope-
promoting interventions.
Hope Interventions
Hope intervention is a valued phenomenon that has the power to bring positive
outcomes to the lives of humans during a crisis. Hope is embraced as a protective
experience for people in challenging conditions. Studies indicate that hope-fostering
strategies in the face of difficult situations have been shown to help individuals in
sustaining, continuing, and enduring life events. Several studies have been conducted to
evaluate the effects of hope intervention in various situations (Zareei Mahmoodabadi et
al., 2019).
Herth (2001) conducted a study to develop and evaluate the Hope Intervention
Program (HIP) based on Hope Process Framework. The study was conducted on a
convenience sample of 38 adults with the first recurrence of cancer who were going
through cancer treatment. The main research variable was to assess the helpfulness of
HIP components in maintaining hope. The HIP was composed of eight sessions to
address four attributes of hope derived from the Hope Process Framework: the
experiential process, relational process, spiritual or transcendent process, and rational
thought process. The HIP was administered over the course of eight weeks, where
participants met as a group for a 2-hour session each week. The entire study lasted for
more than 18 months. Study participants were evaluated at the end of the study, and then

20
at three, six, and nine-month intervals after the last session. Study results indicated that
HIP had a positive impact on participants in rebuilding and maintaining a hopeful outlook
towards life (Herth, 2001).
The elderly phase is a period that can greatly and adversely impact the QOL
because the aging process leads to physical and mental changes that can result in
diminished self-confidence and uncertainty, thus necessitating effective hope
interventions. Zareei Mahmoodabadi et al. (2019) conducted a study using a pre-test and
post-test design to assess the effectiveness of a hope therapy program. The sample
included 24 elderly women in daily care centers with participants divided into two
groups: the experimental group (n=12) and the awaiting group (n=12). The hope therapy
program consisted of eight sessions for the experimental group, and they used the Quality
of Life Scale to measure the impact of the therapy on the experimental group (Zareei
Mahmoodabadi et al., 2019). The researchers compared the hope levels between the
experimental and awaiting groups and found a significant difference between the
populations. The multivariate analysis of variance (MANOVA) analysis used by the
researchers indicated that the depression, anxiety, physical function, mental performance,
and satisfaction in life of those in the experimental group improved significantly after
participating in the hope therapy program. Zareei Mahmoodabadi et al.’s (2019) results
indicated that hope therapy can be an effective intervention for improving the QOL in
elderly populations. The study also showed that elderly individuals can benefit from hope
therapy. Daily care centers should consider instituting hope therapy routinely to improve
QOL outcomes for elderly populations (Zareei Mahmoodabadi et al., 2019).
Hernandez and Overholser (2021) observed that there were limited studies on

21
interventions targeting hopelessness/hope and that most studies targeted associated
constructs like sociality and depression and entail secondary measures of
hopelessness/hope. They conducted a systematic review of hope/hopefulness
interventions for older adults by reviewing existing literature to evaluate the effectiveness
of these interventions. They evaluated 36 studies and concluded that psychological
interventions dependent on life review effectively enhanced hope in various samples
including grieving, depressed, or medically ill patients. Findings also revealed limited
support for exercise programs, education interventions for the ill, exercise for the elderly,
and dignity therapy for patients. Life review-based interventions included self-directed
expression exercises or therapeutic discussions to assist individuals envision their life
from a longitudinal aspect in order to promote hopeful and purposeful meaning in life
(Hernandez & Overholser, 2021).
Knowing that a terminal or serious disease diagnosis can negatively impact the
affected populations significantly, Salamanca-Balen et al. (2021) conducted a systematic
review of the literature on the effectiveness of hope-fostering interventions in palliative
care. Salamanca-Balen et al. (2021) used the Cochrane criteria to assess for bias in the
studies they reviewed. Their review of the literature showed that hope interventions
resulted in increasing hope levels, decreased depression levels, and improved outcomes
in the psycho-spiritual well-being in palliative care patients affected by chronic illnesses.
However, hope did not enhance QOL for palliative care patients (Salamanca-Balen et al.,
2021). While Salamanca-Balenet et al.’s (2021) study highlighted the impact of hope on
improved outcomes in palliative care patients, further research is needed to confirm the
results, especially in elderly populations.

22
Hope and the Elderly
Hope has also been linked to resilience, which can help elderly individuals cope
with the loneliness of living alone. Gupta and Singh (2020) conducted a correlational
study involving purposive sampling to examine the relationship between resilience and
hope in the elderly. The sample included 151 elderly individuals aged 60 to 80.
Researchers used the Connor-Davidson Resilience Scale and Adult Hope Scale to
measure levels of resilience and hope, respectively. The data were analyzed by T-test,
ANOVA, and the Pearson correlation coefficient (Gupta & Singh, 2020). These
researchers found a moderate positive correlation (r= 0.741) between hope and resilience
in the elderly, suggesting that hope can assist older people to meet adverse challenges.
This study also revealed that loneliness played a significant part and was found to be
positively correlated with depression and anxiety and negatively correlated with self-
efficacy, resilience, and psychological and physical health. High resilience, a way of
adapting well to adverse and uncertain circumstances, was strongly associated with
positive outcomes including lower depression levels and increased longevity. The
researchers also found that age, marital status, living standards, the number of family
members and their occupations, among other basic factors, were associated with
resilience and hope; however, gender did not impact resilience and hope. Older people
living alone should be moved to environments where they can interact or have
opportunities to interact with others to help enhance hope and resilience. The study
showed that hope and resilience were related in the elderly population, and resilience
could lead to improved QOL (Gupta & Singh, 2020).
To examine the subjective well-being and hope in the elderly, Gupta and Singh

23
(2019) conducted a correlational study comprised of 151 elderly individuals 60–80 years
of age. The study was designed to compare the well-being and hope levels of
institutionalized and non-institutionalized elderly individuals. The population was chosen
for the study iterate to a mean age of 70.83. Random sampling led to 79 participants from
two nursing homes in Kanpur City, and 72 participants were randomly sampled from
older people living with their families (Gupta & Singh, 2019). Gupta and Singh used the
subjective well-being tool (1992) to measure participants’ well-being or ill-being and they
used the Adult Hope Scale to measure hope levels. Study results revealed that
institutionalized elderly had better overall subjective well-being and scored high for hope
status compared to non-institutionalized individuals (Gupta & Singh, 2019). The results
showed that there was a significant difference in the well-being status between these two
populations. The study also revealed that the mean value of ill-being for non-
institutionalized individuals was higher than that of institutionalized individuals. The
non-institutionalized individuals had limited support from their family members, unlike
institutionalized elderly populations who were scheduled for therapy sessions in their
centers. The researchers concluded that the limited opportunities for interactions for
elderly individuals could result in psychological problems, loss of hope, and induced ill-
being that deters well-being. The institutionalized elderly showed a significant difference
in their levels of hope outcomes, indicating that their environment encouraged wellness-
promoting hope and general well-being. These results indicated the need for family
members to support and comfort the elderly to enhance their hope and improve their
well-being. Aged populations need care and attention for positive psychological
settlement that eventually results in their well-being (Gupta & Singh, 2019).

24
Effects of Hope-Fostering Strategies in Seniors Who Live Alone
There are several methods for fostering hope in seniors such as leaving a legacy,
accomplishing short-term objectives, supporting relatives and friends, turning off your
mind, signs of hope, bright ideas, truthful information from healthcare providers, and
symptom management, among others (Salamanca-Balen et al., 2021). Older individuals
may need different ways of sustaining and nurturing optimism than younger ones. In
addition, it is easy for hope to have a long-lasting impact on the health and well-being of
people throughout their lives. It is a critical psychological resource that assists people
through a range of challenging situations in their lives.
Furthermore, hope has been recognized as a critical component in developing a
feeling of meaning and purpose in one’s life and the improvement of overall QOL in
older people (Salamanca-Balen et al., 2021). As people get older, they often face
cognitive and emotional difficulties and losses in their lives. These difficulties and
failures resulted in their inclusion in assisted care facilities for some of these adults. As a
consequence of moving into long-term care, older people may experience additional
losses, increasing their susceptibility to despair, sickness, and loss of hope. As a result,
finding methods to instill hope in the hearts of senior people is critical in maintaining and
ensuring health and wellness (Salamanca-Balen et al., 2021).
Summary
The literature review for this research revealed a notable association between
hope and QOL. The QOL of the elderly has become a subject of increased research due to
the rising risk of becoming public health threat. Studies indicate that QOL in the elderly
was intertwined with their perceived level of well-being; hence, it was important to

25
provide them with all the resources needed to live a long, quality life. Hope is a vital
force that affects QOL in the elderly and plays an important part in coping and healing.
Several studies reveal the importance of hope-promoting strategies in improving QOL.
The literature review indicates a gap in the knowledge surrounding the effects of hope on
QOL in the senior population. The current study was designed to examine whether there
was improvement in the physical, emotional, and psychological aspects of QOL in the
elderly with a mixed-gender sample after hope therapy.
Conceptual Definitions
Senior People
The senior population is defined as people aged 65 and over (Organization for
Economic Co-operation and Development, 2021; Wayadande & Prabhakar, 2020). For
this research, senior people were defined as those who are 65 years of age and older.
Living Alone
For the purpose of the current study, living alone as seniors who lived in their own
residences, predominantly by themselves.
Quality of Life
Nursing in gerontology and geriatrics ranks QOL as one of the most essential
indicators (Soósová, 2016). The WHO defined QOL as “an individual's perception of
their position in life in the context of the culture and value systems in which they live and
in relation to their goals, expectations, standards and concerns” (Whoqol Group, 1994, p.
11). WHO defined QOL in a broader sense that included physical, mental health, social
relationship, level of independence, and personal beliefs (Wayadande & Prabhakar,

26
2020). Quality of life is the degree to which an individual is healthy and independent and
can participate actively in life events. The current study administered the Older People’s
Quality of Life Questionnaire (OPQOL) scale before and after the interventions to assess
and measure QOL in study participants.
Hope
According to Webster’s Dictionary, hope is a concept of the future: “To desire
with expectation of obtaining fulfillment” (Merriam-Webster, n.d.a). The definition of
hope, according to the Oxford English Dictionary, is “grounds for believing that
something good may happen.” (Gwinn & Hellman, 2019, p. 8.). In current study, hope
was measured by the Herth Hope Index (HHI).
Hope Intervention
According to Webster’s Dictionary, intervention is defined as an action taken to
affect an outcome or improve a situation (Merriam-Webster, n.d.b). Hope intervention is
described as hope-seeking and hope-inspiring strategies that foster hope in individuals
(Herth, 2001). This study utilized the eight-week Hope Intervention Program (HIP)
developed by Dr. K. Herth to enhance hope and QOL in seniors who lived alone. After
implementation of the eight-week program, the hope and the QOL levels were measured
using the HHI scale.
Theoretical Framework
The theoretical framework helps understand the association between interventions
and their effect on people’s overall well-being. Theoretical assertions describe the
relationships that exist among the main concepts of the theoretical model. They aid in

27
developing the appropriate plans and interventions for practice and they also assist in
evaluating the effectiveness of the interventions for further applications (Butts & Rich,
2015). Betty Neuman’s systems model (1972) was used as the theoretical framework for
this project (Alligood, 2018).
Betty Neuman’s Systems Model
Betty Neuman, a nursing theorist, unfolded Neuman’s systems model (1972).
Systems theories such as Betty Neuman’s systems model (1972) are grounded on the
premise that individuals consist of systems that are connected to and influenced by one
another. Two assumptions of this theory are that energy is required to maintain the
harmony in an organizational state, and any dysfunction in one system has an influence
on other systems (Butts & Rich, 2015). The wholistic nature of the model allows for a
wide range of creativity and has been used in a wide variety of healthcare settings.
Neuman’s systems model’s approach to understanding the nature of system
stability and how to prevent system damage made this model an appropriate framework
for the current project. Because of its premises, Betty Neuman’s systems model (1972)
was chosen to guide this study.
Betty Neuman proposed that the person should be treated as a whole system.
Neuman’s systems model consists of four metaparadigm concepts: person, health,
environment, and nursing. This model focuses on the human needs for protection or relief
from stress (de Almeida et al., 2018).
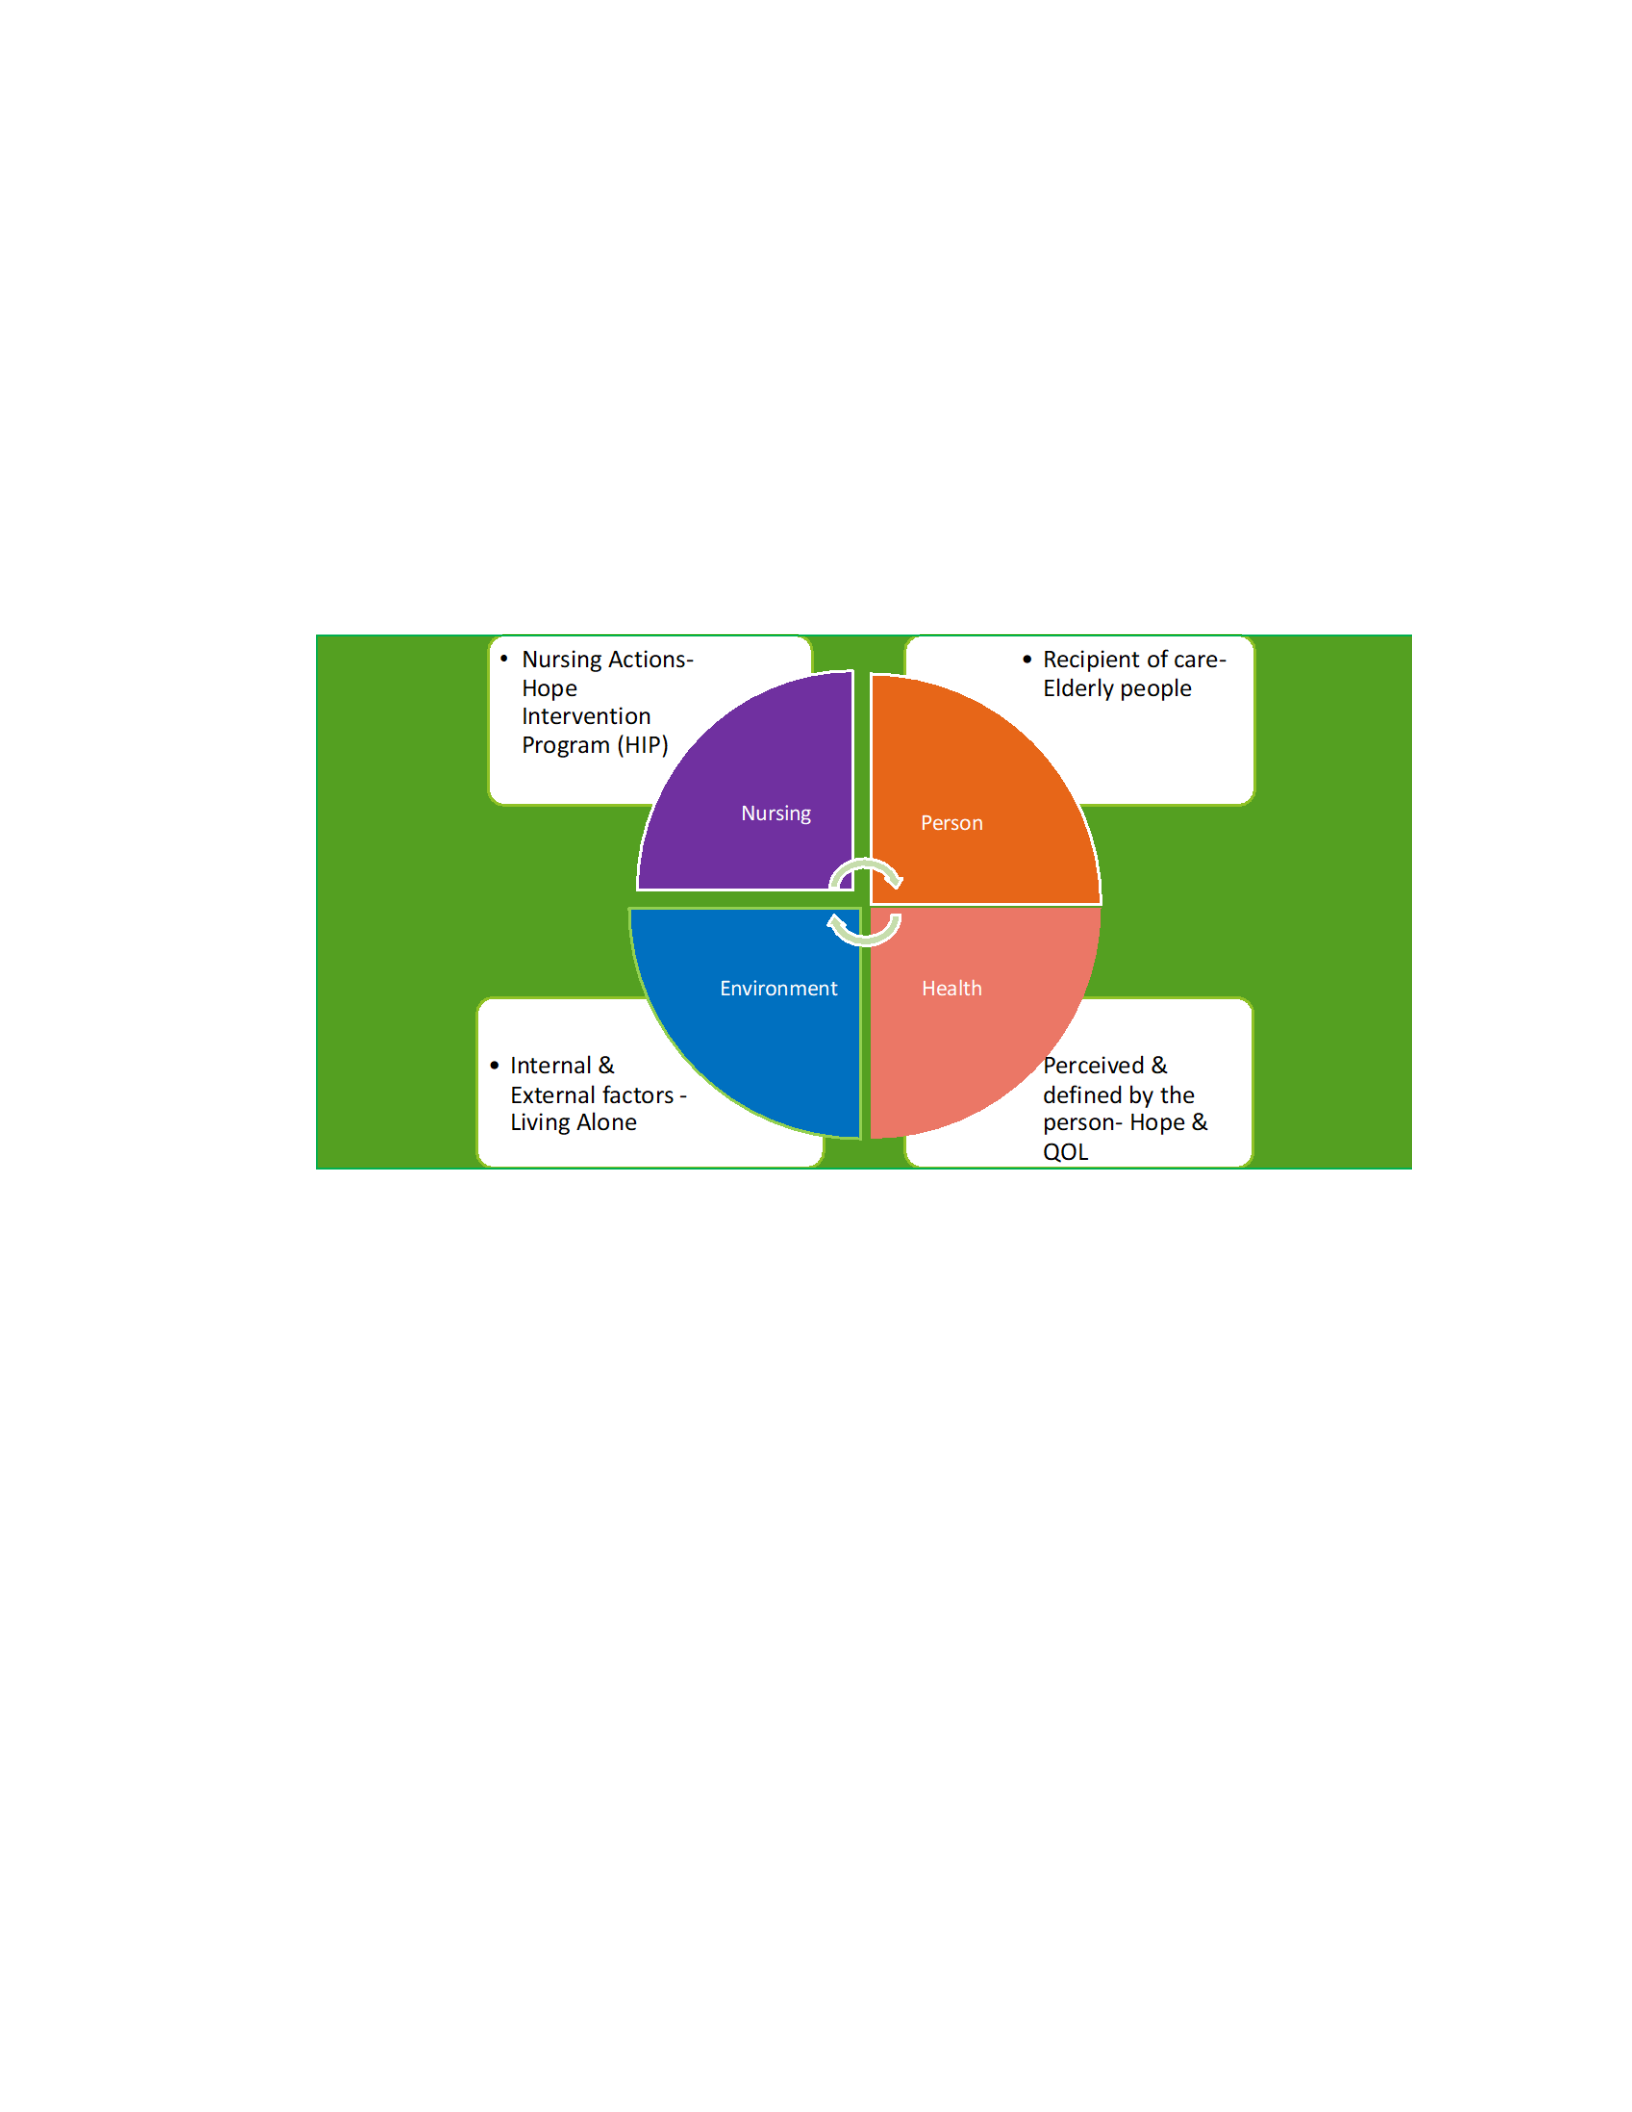
28
Person
Neuman’s model views clients as a whole person with many parts that are in
dynamic interaction with one another (Figure 1). The systems model indicated that five
variables—physiological, spiritual, psychological, socio- cultural, and developmental—
all simultaneously affect the client system (Alligood, 2018; Butts & Rich, 2015).
Figure 1. Neuman’s systems model: Nursing metaparadigm concepts.
The physiological aspect of care pertains to the physical body structure, the socio-
cultural reflects the influence of social and cultural components, the psychological refers
to mental interaction with the environment, the spiritual factor pertains to the influence of
spiritual beliefs, and the developmental component refers to age-related processes and
activities (Ahmadi & Sadeghi, 2017). Because this model focuses on retraining wellness
and ensuring optimal wellness, Neuman classified her systems model as a wellness model
(Alligood, 2018; Butts & Rich 2015).
The purpose and the contents of the HIP in the current study was to provide

29
interventions, keeping in mind the wholistic nature of an individual. The project manager
implemented interventions through HIP that included social, relational, spiritual, and
rational processes to address any impact of living alone on hope levels and QOL in order
to promote wellness in these areas.
Environment
The Neuman (1972) systems model holds that human beings are open systems
that interact with environmental stressors (see Figure1; Alligood, 2018). The environment
is defined as external, created, or internal factors that can affect the system. The internal
environments are found within the system; created environments are developed
unconsciously, while external environments are developed outside the system (Alligood,
2018; Neuman & Fawcett, 2012). The clients are in a relationship with their environment
where they interact with their environment by adjusting to the environment or by
adjusting the environment to themselves (Braga et al., 2018; Cunha et al., 2019).
All factors, whether they are possible or actual responses to stressors, affect
individuals. Stress can be termed as augmenting, inescapable, and painful; it is generally
considered an intuitive state of mind that can be uncontrolled. Neuman’s model focuses
on individuals’ relationship with stress, how to handle it, and its reconstitution (de
Almeida et al., 2018). The major challenge is seeking a solution to eliminate or minimize
the effects of stressors in the system. Interventions should be aimed at maintaining
stability between the environment and the variables of the clients (Alligood, 2018).
Neuman described that adjustment is a process by which individuals meet and satisfy
their needs. Since many needs are present that can affect stability and balance, the
adjustment process is dynamic and continuous.

30
Aging poses greater challenges and living alone can contribute to the exacerbation
of underlying issues affecting the level of hope, outlook towards life, and the QOL in
seniors. Stigmatization and isolation are external factors that trigger stressors in senior
people. These stressors can further lead to created and internalized environments of
loneliness, which can then affect their level of hope and QOL and pose serious health
risks. This study proposed to examine the effects of HIP that can assist in this process of
adjustment. The HIP interventions to establish a caring and supportive environment and
build a sense of community through interventions addressed some of these challenges of
improving the level of hope and QOL in senior population.
Health
Neuman considered her system theory as a wellness model. She defined health as
energy that yields the highest quality system stability at any point. Neuman perceived
health as a continuum or scale of wellness to sickness, which is dynamic and always
subject to change. According to the model, there is optimal wellness (negentropy) when
the system’s needs are met; when they are not met, there is sickness, and when there is
insufficient energy to support life, then death results (entropy; Alligood, 2018).
Every participant in the study had a unique system. If adaptation to the changes
and challenges that came as a result of living alone were not stable, they could experience
a breach in the continuum of the system leading to less-than-desired levels of wellness.
Through HIP, the project manager promoted the individual’s system stabilization through
acquirement, retention, and maintenance of optimal wholeness and wellness in the
participants (de Almeida et al., 2018). Through HIP, the sense of hope level and QOL
which pertain to the health and wellness spectrum may be improved and maintained in

31
addition to stabilization of the wellness system.
Nursing
According to Neuman’s philosophy, nursing is a unique profession that is
concerned with all the factors affecting the individual and thus believes in the importance
of providing the wholistic approach (Akhlaghi et al., 2021). In this model, the nurse is
considered a key participant with the client; the nurse is interested in assessing how the
clients are affected by environmental stressors such as living alone, as in this study. The
seniors adjust to living alone by accepting their state of decreased mobility and loss of a
loved one, among other factors. The nursing interventions link four main concepts of this
model: people, environment, nursing, and health (Braga et al., 2018; Cunha et al., 2019;
see Figure 1). Nurses play an important role in creating a relationship among individuals,
health, and the environment to prepare individuals to adapt to the life changes in order to
improve and maintain the QOL (Akhlaghi et al., 2021).
Lines of Defense
In her system-based model, Betty Neuman described other components: stress,
systemic feedback loop, and lines of defenses. Neuman also emphasized that the lines of
defense are protective mechanisms that reflect how the individual or system adapts after
adjusting to the stressors. These lines of defense include the flexible line of defense,
normal line of defense, and lines of resistance (Alligood, 2018).
Flexible Line of Defense
The flexible line of defense is the outer layer, and it is the protective mechanism
that surrounds and protects the normal line of defense from invasion by various stressors.

32
It is dynamic and can be quickly changed in response to these stressors. The relationship
of the physiological, spiritual, psychological, socio-cultural, and developmental variables
can affect an individual’s response to the stressors. It is important that the flexible line of
defense be strengthened to prevent possible future damage (Alligood, 2018; McEwen &
Wills, 2014).
The Normal Line of Defense
This is the model’s middle layer. It reflects a stable state that the individual or
system adapts to after the adjustment to stressors. This stability is the result of an
individual’s lifestyle, coping behaviors, and developmental stage. It becomes a standard
for the wellness-deviance determination of clients in the system (Alligood, 2018;
McEwen & Wills, 2014).
Lines of Resistance
This is the innermost layer that represents protective mechanisms that are
activated when there is a penetration of the normal line of defense due to stressors in the
system such as the immune system response to the stressors (Alligood, 2018). According
to Neuman (as cited in Alligood), this state symbolizes a movement to an illness on a
wellness-illness continuum. However, when there is sufficient energy, the system can be
reclaimed by restoring the regular defense line below, at, or above its initial level
(Alligood, 2018).
Neuman emphasized that in order to deal with these stressors, different
interventions at different levels, such as primary, secondary, and tertiary interventions, are
needed. The primary intervention occurs before the system is invaded, the secondary

33
intervention occurs after the system has been invaded, while the tertiary intervention
occurs during the reclamation process (de Almeida et al., 2018).
The stressors that are mainly found in senior people could range between fear,
worry, anxiety, and frustration. In addition, a variation in the organic system could also be
a source of intrapersonal stressors. Interpersonal stressors also occur between individuals
due to various reasons causing relationships strain (de Almeida et al., 2018). According to
Neuman, extra personal stressors occur due to external environmental factors which are
often found outside the client’s boundaries at the proximal range, such as living alone in
this study (Alligood, 2018).
Nurses are active contributors in prevention strategy since it is considered one of
the most important interventions in protecting the individual while providing care. In this
study, primary, secondary, and tertiary interventions through HIP were aimed at
equipping the seniors with strategies to tackle the stressors that attempted to attack their
lines of defense. Nurses play a pivotal role in taking care of the senior people in society,
especially those who are isolated and do not have family or social support. It is important,
therefore, for nurses to determine how stressors affect the systems of seniors, ultimately
affecting their QOL. The Newman systems model has a broad application in current and
future nursing practice. The use of this model by nurses and practitioners can provide
wholistic, unified, and goal-oriented client care (Gale, 2020).

34
CHAPTER 3
METHODOLOGY
This research was a two-group experimental study conducted with pre- and post-
test interventions. The study participants included the vulnerable population; therefore,
every precaution was taken to keep the participants safe during the study.
PICOT Question
The literature review shows the adverse effects of living alone on senior peoples’
overall well-being. Studies indicate that these detrimental effects can be eliminated or
minimized through strategies that promote a sense of well-being in this population. Hope-
fostering interventions and programs aim to promote overall well-being in a variety of
populations and also various settings such as educational centers, therapy, counseling,
recreational organizations, and correctional facilities. Studies reveal that hope-fostering
interventions enhance psychosocial outcomes and reduce depression. These interventions
are aimed at addressing participants’ strengths and the strengths they hope to develop
more (Larsen et al., 2015; Leontopoulou, 2020). Based on the previous literature
findings, the current study PICOT question was developed.
The guiding PICOT question for this study was as follows: In seniors 65 years
and older who live alone, how does the implementation of eight-weeks hope intervention
compared to seniors 65 years and older who live alone and do not receive the hope

35
intervention affect the level of hope and quality of life?
Hope Intervention Program
The HIP that the current study implemented was developed by Dr. K. Herth in
2001. The HIP is composed of eight sessions to address four attributes of hope derived
from the Hope Process Framework: experiential process, relational process, rational
thought process, and spiritual or transcendent process. The HIP was administered over the
course of eight weeks where the participants met as a group for a 2-hour session each
week (Herth, 2001; see Appendix A). The literature suggests that the length of time must
be sufficient (e.g., 7–10 weeks) for the study to be effective and bring changes in the
participants which have been shown to continue for a longer time afterward (Herth,
2001). The current study administered this program just as it was administered, over an
eight-week period, and evaluated the effects of HIP on the level of hope and QOL in
seniors who lived alone.
Project Design
In the current scholarly project for HIP and its effect on the level of hope and
QOL in senior people who live alone, a two-group experimental study design was
applied. An experimental design was applicable because the participants were randomly
assigned to experimental and control groups (Bordens & Abbott, 2008). All qualified
participants (see Appendix B) completed Herth Hope Index (HHI) and OPQOL scale
both at the inception and again at the end of the eight-week HIP, which was the
independent variable applied in order to assess the measure the of level of hope and QOL,
the dependent variables. The HIP was then implemented in the form of in-person group

36
therapy for those who were in the experimental group; during this time, they participated
in weekly hope-fostering activities through discussion and hope-engendering exercises.
The final phase of the study constituted a post-test to all participants to examine the
participants’ level of hope and a post-test to re-examine their QOL at the conclusion of
the interventions.
Recruitment
For this project, participants were recruited from the local community. Flyers for
the project were distributed in local community senior centers, health and wellness
clinics, churches, grocery stores, restaurants, and Public Health Department. Prior to the
participants’ consent, the project manager conducted an informational meeting to
introduce the project with the invitation to join the study.
Population and Sample
Population
The population of interest corresponded to elderly participants who lived alone.
The sample consisted of elderly participants selected from the general community in
Southwest Michigan.
Inclusion Criteria Included
a. Participants 65 years or older
b. Participants who lived alone in their residences
c. Participants who spoke English and were able to read and write English
d. Participants who scored 0-2 on Eastern Clinical Oncology Group (ECOG)
performance status screening (see Appendix C)
37
Exclusion Criteria Included
a. Participants who were bedbound
b. Participants who had any mental illness
Sample/Power Analysis
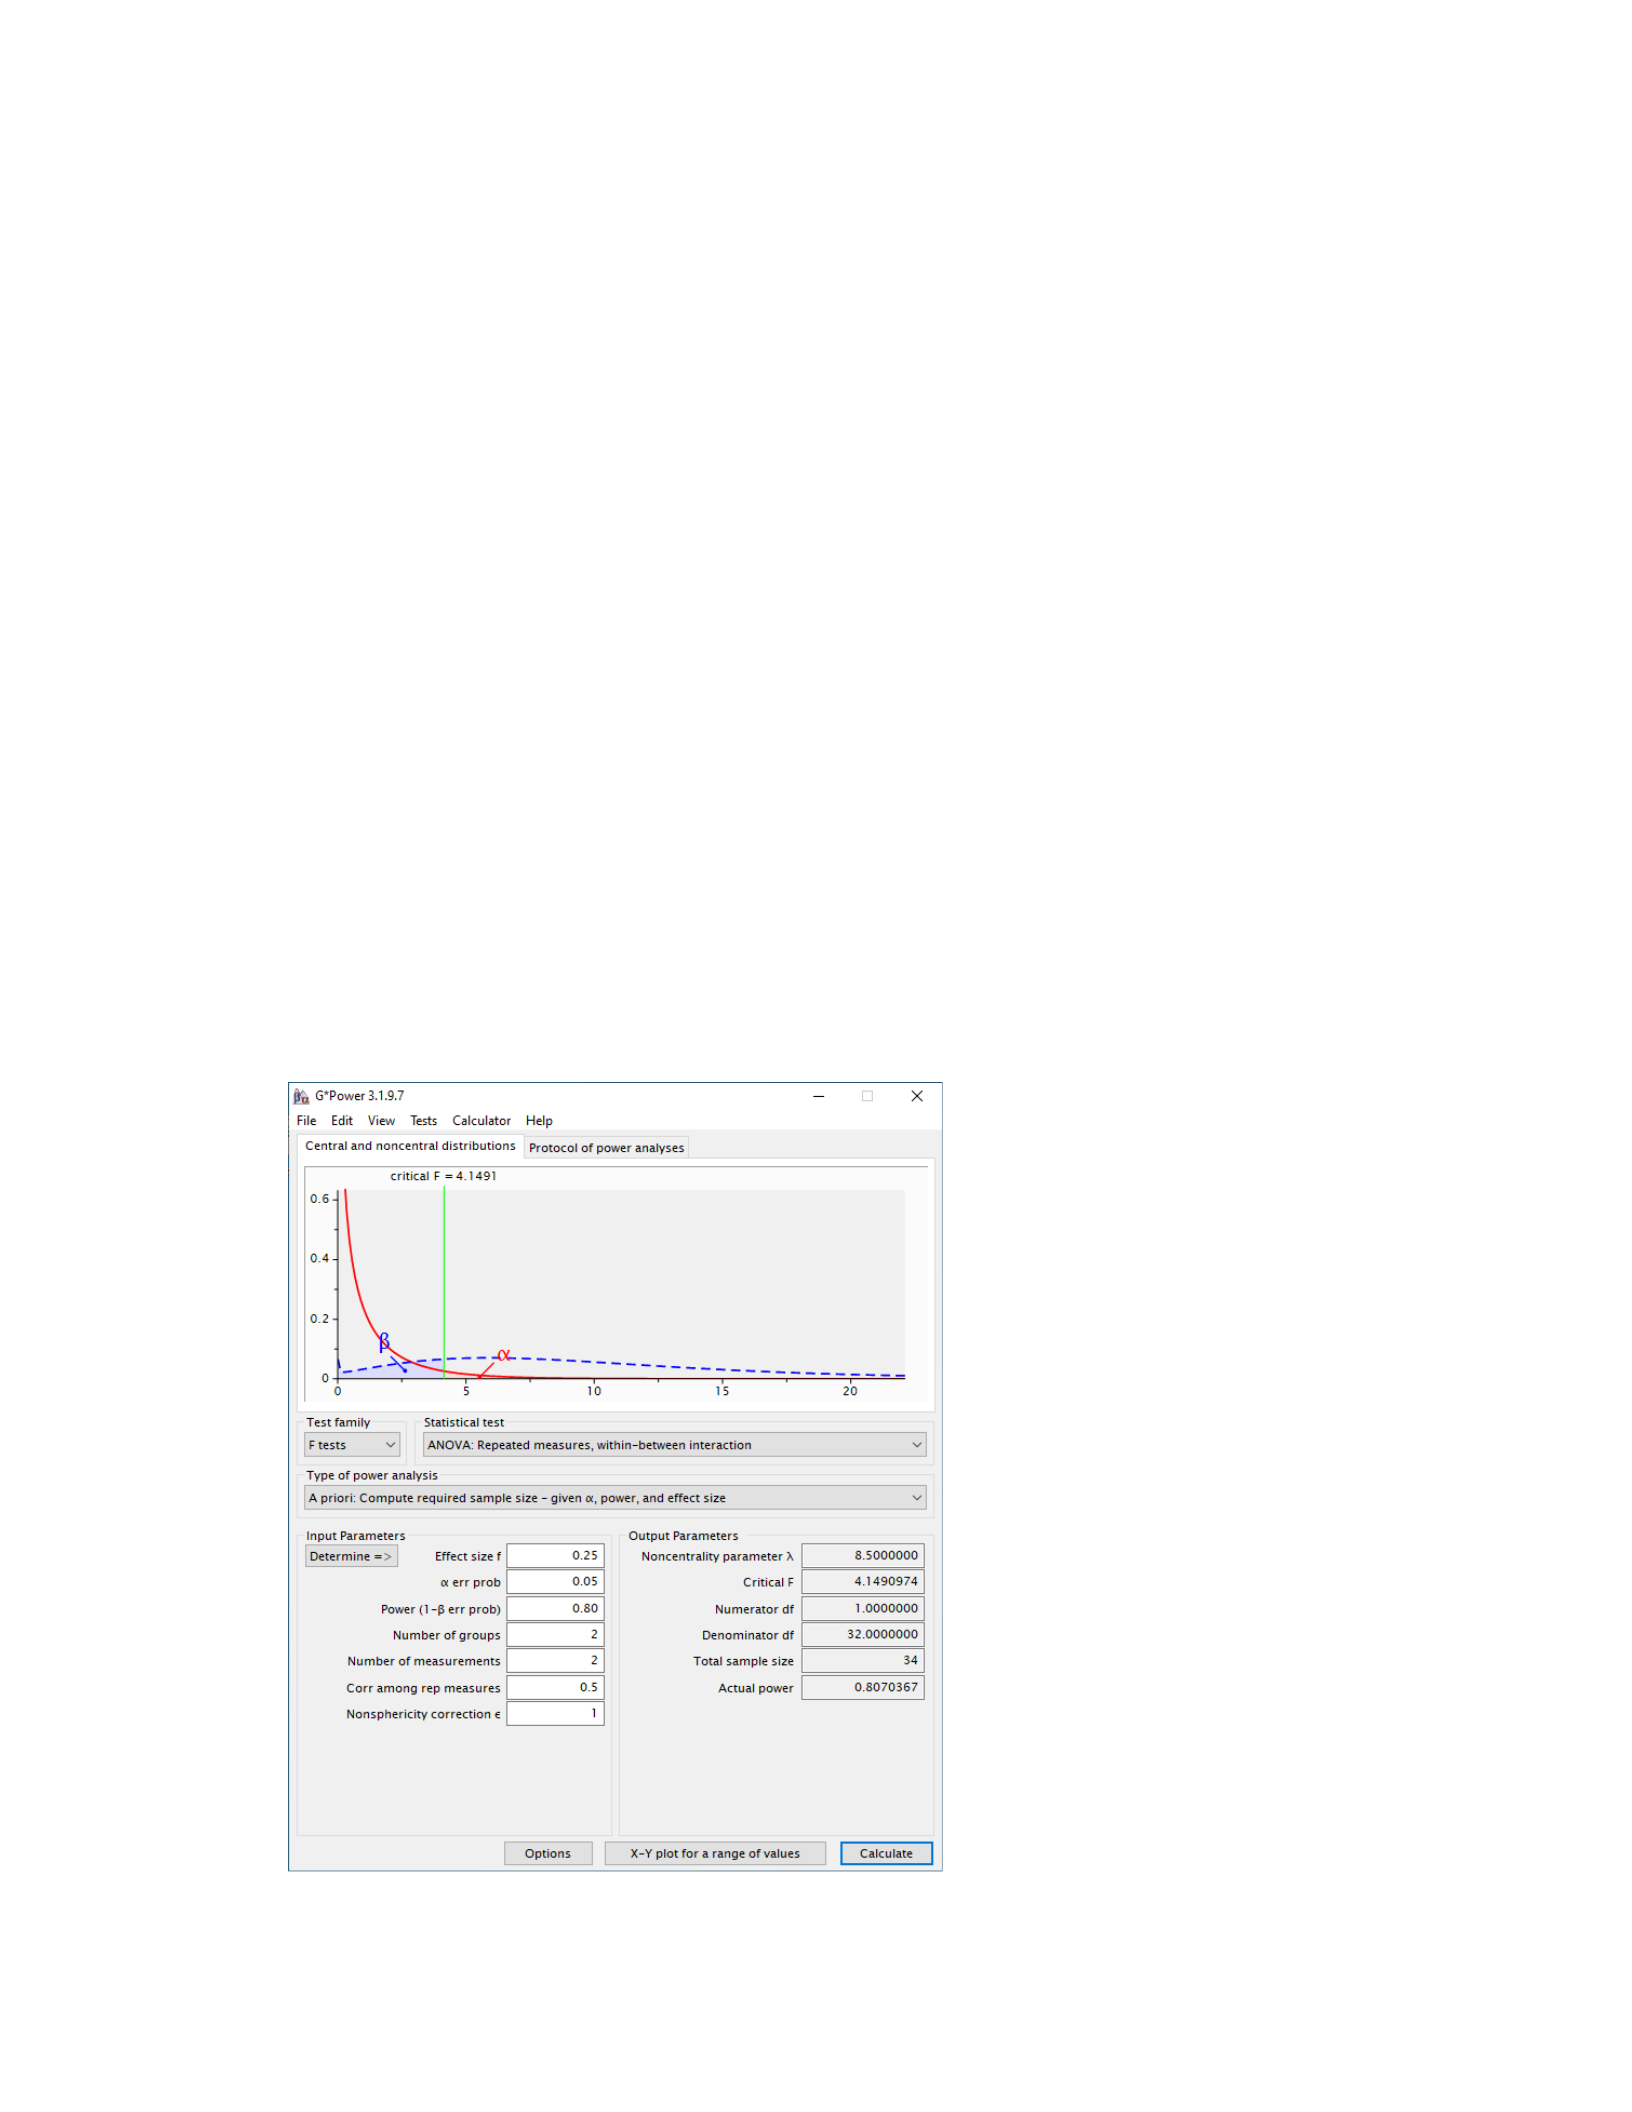
The study design was developed through consultation with a statistician. A power
analysis was conducted in G*Power 3.1.9.7 to determine the minimum sample size
requirement (Faul et al., 2014). By applying the use of a mixed model ANOVA and
utilizing a medium effect size (f = 0.25), a two-group, a pre-test-post-test comparison, a
significance level of .05, and a power of .80, it was determined that a minimum of 34
participants would be sufficient for the data collection (approximately 17 participants in
each group), as seen in Figure 2.
Figure 2. Power analysis for mixed model ANOVA.

38
Instruments, Interventions, Procedure, and Data Collection
Instruments
The current study utilized two instruments: The HHI and the OPQOL to measure
hope and QOL in the selected population.
Herth Hope Index
The HHI (see Appendix D) was developed to assess hope in adults in clinical
settings (Herth, 1992). The HHI consists of 12 survey items using a four-point Likert
scale ranging from (1 = Strongly Disagree to 4 = Strongly Agree). Permission was
granted to administer the HHI from the original author, Dr. Kaye Herth (see Appendix E).
The HHI has been translated into a variety of languages. Construct validity has been
established with the HHI through the use of an exploratory factor analysis (EFA) with a
varimax rotation. The results of the EFA identified a three-factor solution with
approximately 61% of the variance being explained by the factors (Herth, 1992). The
three factors correspond to an individual’s perception of present and future, inner
optimistic readiness, and interconnectedness with self and others. Reliability of the scales
was established with the Cronbach’s alpha test of internal consistency. Cronbach’s alpha
coefficients for the three scales ranged from .78 to .86. For the purpose of this research,
the overall scale for hope was utilized. Scoring consisted of adding the points for the total
scale. Hope was a measurable, continuous variable with possible scores ranging from 12-
48 points. The higher score indicates a higher level of hope (Herth, 1992).
Older People’s Quality of Life
Questionnaire Scale
The OPQOL (see Appendix F) is a 35-item survey designed to measure older

39
populations’ QOL. The OPQOL utilizes a five-point Likert scale ranging from 1 (strongly
disagree) to 5 (strongly agree). The survey has established both acceptable reliability and
validity. Cronbach’s alpha test of internal consistency met the acceptable threshold,
ranging between .70 and .90 for multiple samples (Bowling, 2009). Convergent validity
was established with significant correlations between age, marital status, and QOL. A
principal component analysis (PCA) revealed approximately 60.58% of the variance in
QOL could be explained by a nine-factor structure (Bowling, 2009). The QOL variable
was computed through a composite score of the respective items. Quality of life was a
measurable, continuous variable with possible scores ranging from 35-175 points. The
higher score reveals higher level of QOL.
Interventions
Group intervention for the experimental group consisted of an 8-session hope
intervention protocol adapted from the HIP by Dr. Kaye Herth. The program took place
over an eight-week period. Each session was conducted over a 2-hour period. Each
session content, activities, and exercises were as follows (Herth, 2001; see Appendix A
for more details):
• Session 1: (a) Overview of sessions and (b) getting acquainted exercises.
• Session 2: (a) Discuss the meaning of hope and hope as active waiting, (b)
discuss the dialectic relationship between hope and hopelessness, and (c) discuss threats
to hope.
• Session 3: (a) Develop a hope mantel and (b) begin a hope journal, tape, or
drawing to chronicle one’s hope journey.

40
• Session 4: (a) Discuss the reciprocal/interdependent nature of hope, (b)
discuss the role of family and friends in the hope journey, (c) discuss community
resources, (d) develop a list of one’s hopelets, and (e) develop a hope energy-savers
basket.
• Session 5: (a) Discuss and implement value clarification exercises (focus on
values thought important and usual sources of strength), (b) discuss and share possible
spiritual resources, (c) implement life awareness activities, (d) develop a joy collage, and
(e) discuss photos/pictures that represent hope.
• Session 6: (a) Discuss reality surveillance and goal setting as it impacts hope,
(b) discuss success mapping, (c) develop a hope kit, (d) discuss and practice a variety of
cognitive reframing strategies, and (e) discuss the role of past memories on hope.
• Session 7: (a) Begin a hope memories book, (b) discuss the role of nature in
hope, and (c) discuss the value of lightheartedness and how to engender more in one’s
life (e.g., funny bone exercises).
• Session 8: (a) Share current and potential future use of the hope mantel and
the hope journal, tape, or drawing; (b) discuss a hope engendering and maintenance plan;
(c) develop a phone, e-mail, or chat room networking system; and (d) complete the
program evaluation tool.
Procedure and Data Collection
The procedure for the study was as follows. After the successful proposal defense,
Andrews University Institutional Review Board (IRB) approval was obtained (see
Appendix G). Invitation flyers (see Appendix H) for the study were placed in the local
community senior centers, wellness-clinics, grocery stores, restaurants, and Public Health

41
Department for 4 weeks prior to the beginning of the study. The purpose of the flyer was
to advertise the opportunity of participating in the research study and briefly introduce
the study focus. The invitation flyers consisted of project manager’s contact information
including mobile phone number. Interested participants were asked to contact the project
manager by calling the phone number provided on the flyer.
Two weeks before the implementation of the program, a face-to-face interview
with participants was conducted at the local wellness clinic. These local clinics were
chosen because of their proximity to the center of town. Strict clinic guidelines according
to the Health Department were followed during each meeting.
During the initial contact, informed consent (See Appendix I) was obtained after
explaining the study and answering participants’ questions. The consent form outlined the
purpose of the study, inclusion and exclusion criteria, and the estimated time frame for
completion of the study. The participants provided consent to continue with the survey
process.
Upon providing consent, the participants were directed to the screening for the
inclusions criteria of the study. The participants who did not meet the inclusion criteria
were removed from the study. Qualifying participants were then asked to respond to a
demographic survey (See Appendix J). Following the demographic survey, the HHI
survey and OPQOL were administered as pre-tests for the baseline. Assistance was
provided as needed to answer and appropriately complete the survey if the participants
did not understand the questions.
A random identifier was assigned to each participant. Using the Excel command,
RANDBETWEEN, the participants were then randomly assigned to experimental (coded

42
1) and control groups (coded 0). After the last session of the hope intervention in Week 8,
the project manager administered the HHI and OPQOL surveys as post-tests to both
experimental and random groups via pen and paper. The post-test responses were
matched to the pre-test through the random identifier assigned to each participant.
Finally, a token of a $25.00 gift card was given to each participant who completed the
study.
Data Analysis Plan
The data were uploaded into the SPSS version 27.0 for Windows. Participants
who did not respond to the full HHI and OPQOL questionnaire were removed from
further analysis. Frequencies and percentages were used to summarize the demographic
variables such as gender and ethnicity. A series of chi-square tests of independence were
used to assess for differences in the demographic distribution based on random
assignment to treatment and control groups. A chi-square analysis is used when the
strength of the relationship between two nominal-level variables are tested (Pallant,
2020). In addition, percentages and frequencies were examined for the most and least
helpful intervention activities. Means and standard deviations were used to examine the
trends of the continuous-level variables such as the HHI and OPQOL scales. Cronbach’s
alpha test of internal consistency and reliability were reevaluated for the hope and QOL
scales. The strength of the alpha values was interpreted through the use of George and
Mallery’s (2020) guidelines, in which α < .5 Unacceptable, α > .5 Poor, α > .6
Questionable, α > .7 Acceptable, α > .8 Good, and α > .9 Excellent.
Inferential analyses were used for the research. In order to address the PICOT
question, two independent sample t-tests were first conducted to analyze for baseline

43
differences in level of hope and QOL between the experimental and control groups. Two
additional independent sample t-tests were conducted to analyze for post-test differences
in level of hope and QOL between the experimental and control groups. Two mixed
model ANOVAs were conducted to assess for differences in hope and QOL before and
after the intervention and between the experimental and control groups. A mixed model
ANOVA is appropriate when testing for differences in a continuous variable over time
and between groups (Pallant, 2020). Before analyzing the data, the assumption of
normality was tested with Shapiro-Wilk tests. Homogeneity of variance was tested with
Levene’s test. The non-parametric Wilcoxon-Signed Rank tests were intended to be
conducted to test for differences in hope and QOL between pre-test and post-test if the
assumption of normality was not met.
The mixed model ANOVA examined three effects: the within-effect, the
between-effect, and the interaction effect. The within-effect tested for differences
between pre-test and post-test. The between-effect tested for differences between
experimental and control groups. The interaction effect tested for differences over time
and between groups, simultaneously. Statistical significance was evaluated at the
generally accepted level, α = .05.
Ancillary Analysis
A Pearson correlation was conducted to assess the strength of the relationship
between hope and QOL. The Pearson correlation was an ancillary test because the
analysis was a separate examination from the PICOT question and the mixed model
ANOVA. A Pearson correlation is appropriate when testing the strength of the association
between two continuous-level variables (Pallant, 2020). Prior to analysis, the assumptions

44
of normality and linearity were tested on the data. Linearity was visually assessed with a
scatterplot between hope and QOL. If the assumptions were not supported, a non-
parametric Spearman correlation was planned to be conducted as an alternative.
The Pearson or Spearman correlation coefficients can range from 0 (no
relationship) to +1 (perfect positive linear relationship) or -1 (perfect negative linear
relationship). Positive correlation coefficients reveal a direct association, meaning that as
one variable increases, the other variable also shows improvement. Negative correlation
coefficients identify an inverse relationship: as one variable increases, the other variable
decreases. Cohen’s standard (Cohen, 1988) was used to evaluate the correlation
coefficient to determine the strength of the relationship where coefficients above .50
represent a large association; coefficients between .30 and .49 represent a medium
association; and .10 and .29 represent a small association.
Confidentiality
Confidentiality was ensured by randomly identifying the participants without
using their personal identifying information. The study assigned a random identifier to
each participant through the use of the Excel command, RANDBETWEEN, to administer
the surveys and collect the data. All the information was placed in a secure place
accessible only with a secure password by the project manager. The data will be kept for
5 years and then will be destroyed from both computer and external hard drives.
Project Timeline
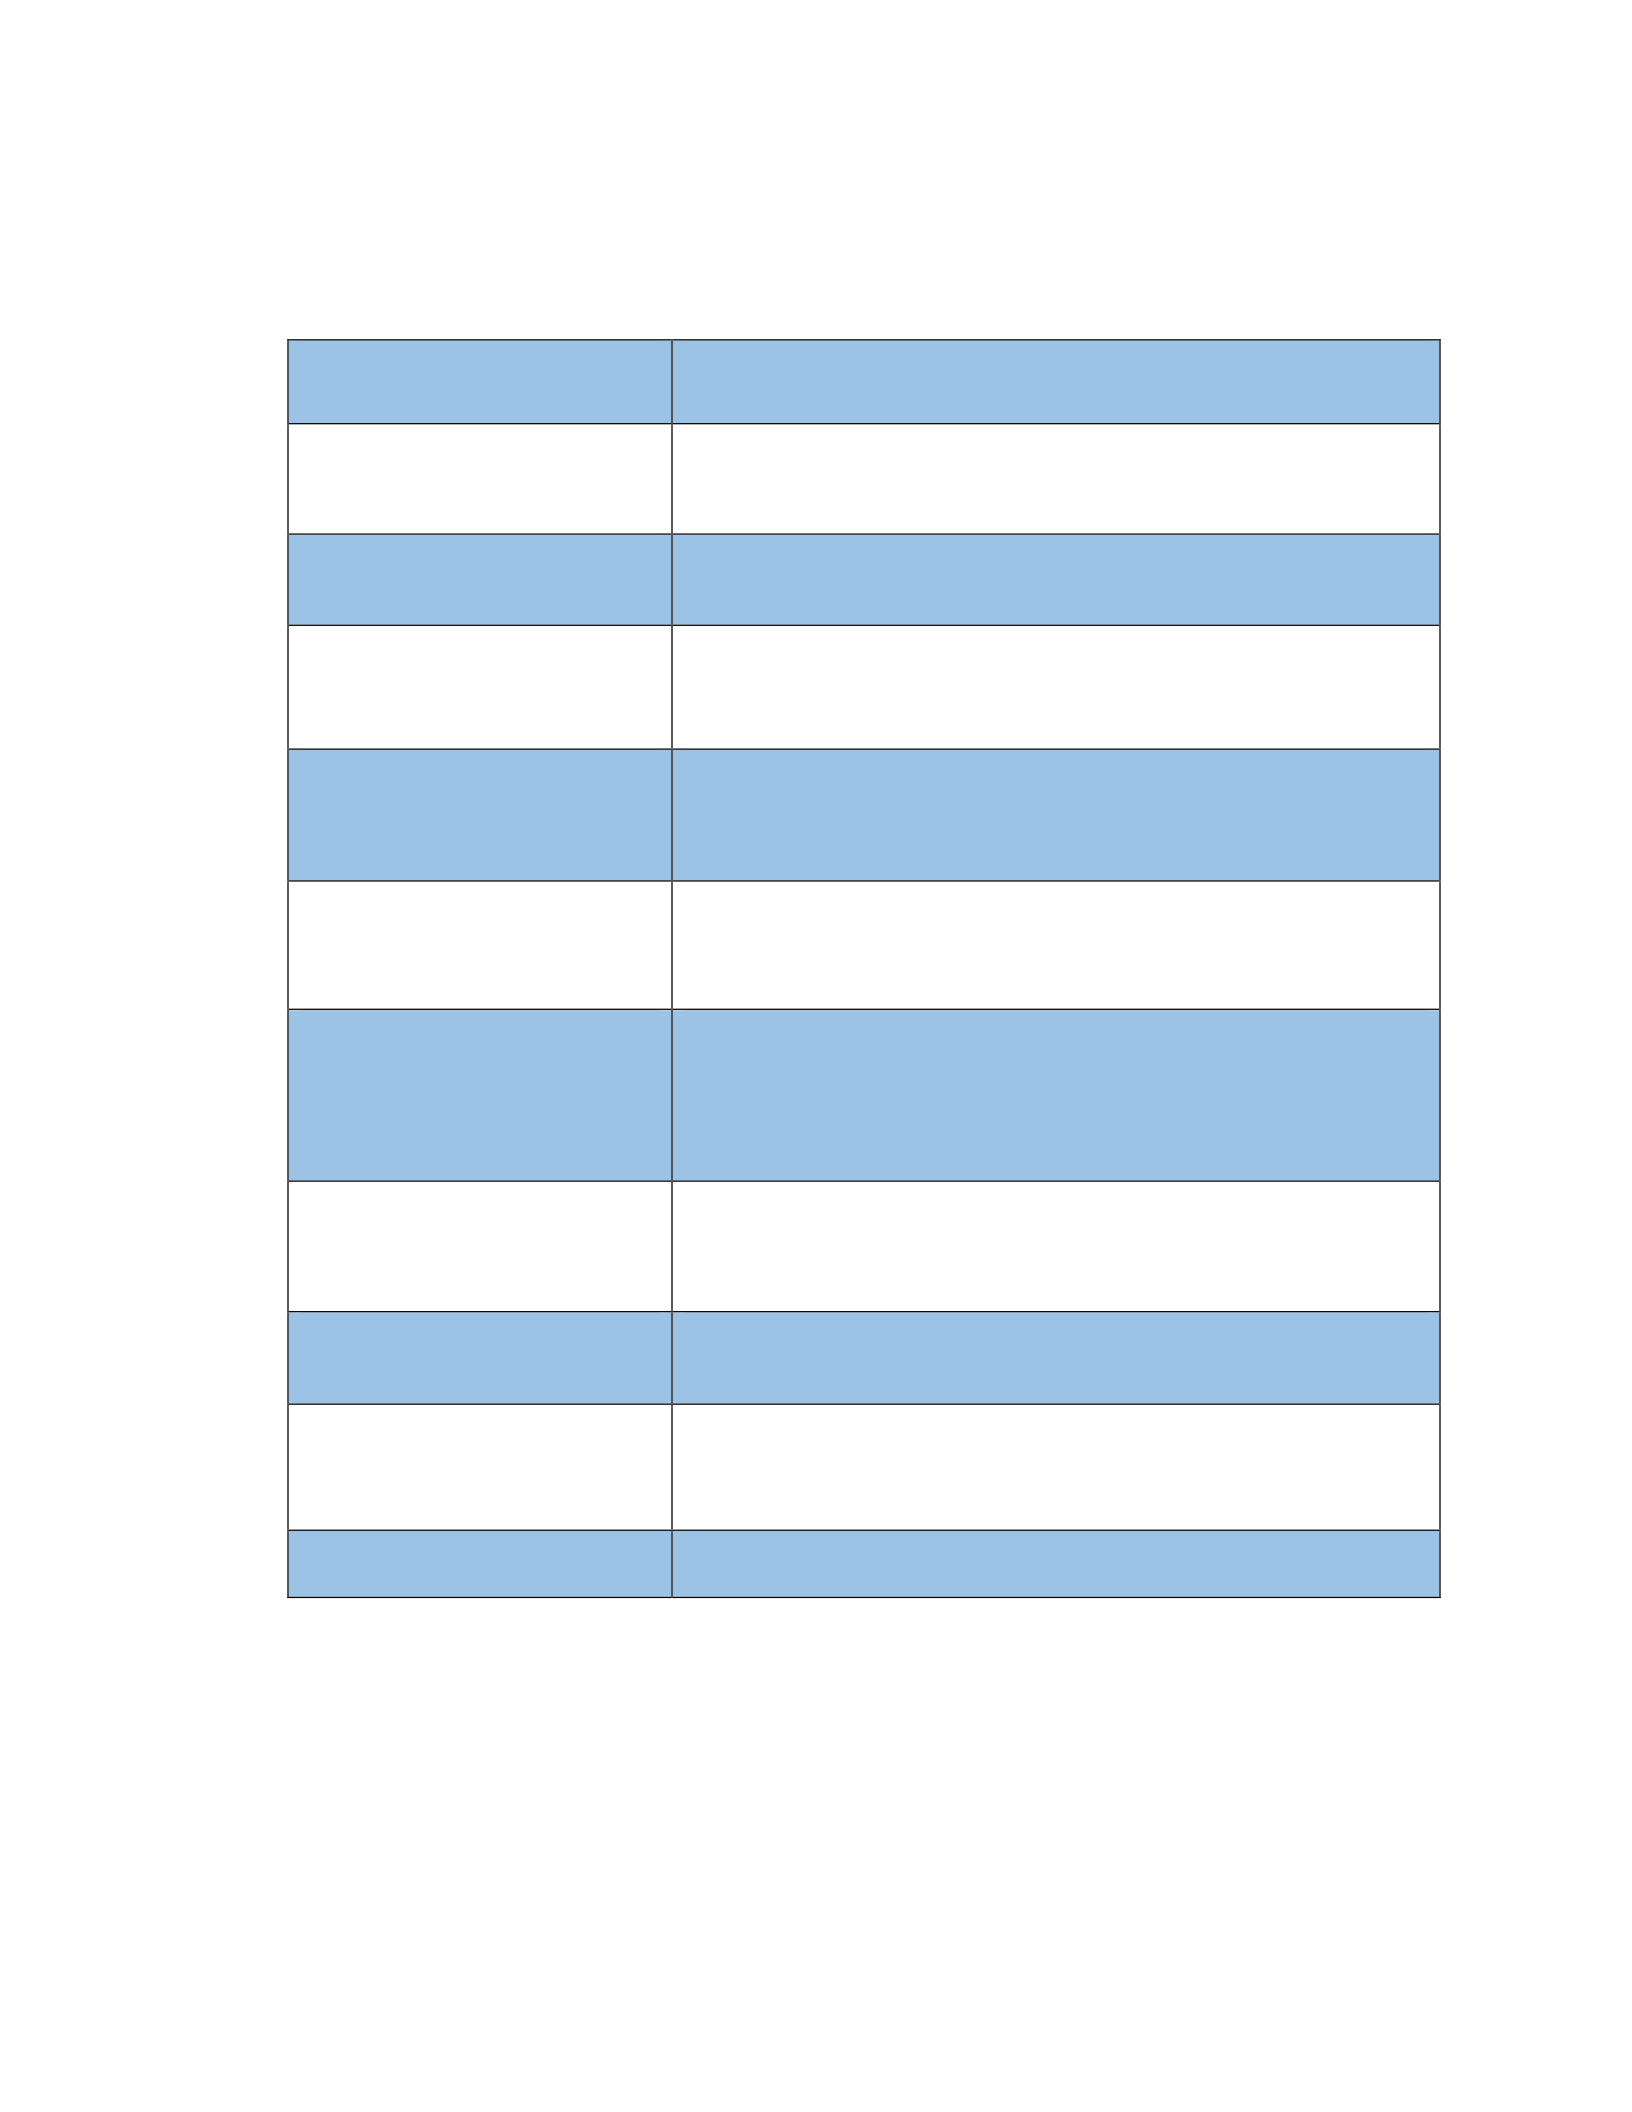
Table 1 below outlines the timeline of the project from its commencement to its
end.
45
Table 1
Project Timeline
Timeline Dates
Events
April 4th-April 21st, 2022
Recruiting process. Demographic, ECOG surveys/Pre-
tests (HHI & OPQOL) data collection.
April 25th-April 28th, 2022
Session 1: Building a sense of community. Introduction
to the program, getting acquainted with HIP exercises.
May 3rd-May 4th, 2022
Session 2: Searching for hope/experimental process.
Discuss meaning of hope and identify areas of hope in
life.
May 9th-May 11th, 2022
Session 3: Searching for hope/discuss threats to hope.
Develop a hope mantel and begin a hope journal (see
Appendix A).
May 16th-May 18th, 2022
Session 4: Connecting with others/relational process.
Discuss the role of family & friends. Discuss community
resources.
May 23rd-May 25th, 2022
Session 5: Expanding the boundaries.
Spiritual/transcendent process. Discuss value
clarification exercises. Share possible spiritual resources.
Develop joy collage.
May 30th-June 1st, 2022
Session 6: Building the hopeful veneer/rational thought
process. Discuss cognitive reframing strategies, role of
hope in past memories. Develop hope kit.
June 7th-June 8th, 2022
Session 7: Building the hopeful veneer. Discuss the role
of nature and lightheartedness
June 13th-June 15th, 2022
Session 8: Reflecting and evaluating. Post-test data
collection. Project evaluation. Gift-card given with
thanks.
August-November, 2022
Analysis and write up

46
CHAPTER 4
RESULTS
The purpose of this project was to evaluate the effects of a non-pharmacological
intervention, in this case, the utilization of hope interventions on hope and on the QOL in
senior people who live alone. In this chapter, the findings of the data analyses are
presented. Frequencies and percentages were used to describe trends in the demographic
data. Cronbach’s alpha test of reliability was used to evaluate the internal consistency of
the measures. To address the PICOT question, two mixed model ANOVAs were
conducted to evaluate for differences in level of hope and QOL following the
intervention. Ancillary analyses were conducted to test for the relationship between level
of hope and QOL.
Data Collection
After receiving approval from Andrews University IRB, a total of 200 project
invitation flyers (see Appendix H) for the study were sent out and placed in the local
community senior centers, wellness-clinics, grocery stores, restaurants, and Public Health
Department for 4 weeks prior to the beginning of the study. A total of 43 individuals from
the general community in Southwest Michigan approached the project manager to learn
more about the research project and to participate in the study. Nine individuals declined
to take part in the study after learning the length of the program. Thirty-four participants

47
decided to enroll in the project and signed the informed consent.
During the initial screening, three participants were excluded from the study. Of
those three participants, two individuals did not meet the criteria for living alone. One
participant was 64 years old, which was lower than the inclusion criteria for being at least
65 years old. A total of 31 participants completed the demographic and pre-test HHI and
OPQOL surveys using the pen and paper. The Excel command, RANDBETWEEN, was
used to randomly assign participants to the experimental or control groups. The
RANDBETWEEN function works by randomly selecting an integer between two
numbers. Using this command, study adults were randomly assigned to experimental
(coded 1) and control groups (coded 0). After pre-test data collection, participants in the
control group were asked to return after 8 weeks to complete the post-test. I recorded the
pre-test survey scores electronically on the Excel spreadsheet.
The experimental group consisted of 16 participants and the control group
consisted of 15. However, three individuals from the experimental group did not
complete the intervention in its entirety and only attended part of the program. Two
additional participants dropped out of the intervention program due to illness. Thus, these
participants were excluded from the final data analysis. Three participants from the
control group did not return to complete the post-test, so they were excluded from the
final data analysis (see Figure 3).
48
Figure 3. Participant flow chart.
Data Analysis
Frequencies and percentages were used for the nominal variables. Chi-square tests
were conducted to examine the strength of the relationships of the nominal-level
variables by experimental and control groups. There were no statistically significant
differences in the demographic variables between the two groups. The age variable was
not listed because the participants were recruited based on whether participants’ age was
Individuals Approached n=43
Excluded
n=9 declined to participate
n-2 did not live alone n=1 64 years old
Randomized n=31
Control group
n=15 randomized
Excluded n=3 no post-survey
Analyzed n=12
Experimental group
n=16 randomized
Excluded n=5
(2 dropped out & 3 did not attend the
HIP 100%)
Analyzed n=11

49
65 or higher or not. The finding of the chi-square test between ECOG and group was
statistically significant, χ2(2) = 7.11, p = .029. Table 2 presents the findings of the cross-
tabulations. Figure 4 provides details of participants in both groups for ECOG.
Table 2
Cross-Tabulation between Nominal Variables and Group
Group
Variable
Experimental
(n = 11)
Control
(n = 12)
χ2
p
Gender
0.96
.328
Male
0 (0.00%)
1 (8.33%)
Female
11 (100.00%)
11 (91.67%)
Ethnicity
0.01 .949
Black or African American
1 (9.09%)
1 (8.33%)
White
10 (90.91%)
11 (91.67%)
Marital Status
1.29 .524
Single
1 (9.09%)
0 (0.00%)
Divorced
5 (45.45%)
5 (41.67%)
Widowed
5 (45.45%)
7 (58.33%)
Educational Level
1.05 .592
High school graduate
6 (54.55%)
5 (41.67%)
College graduate
4 (36.36%)
4 (33.33%)
Graduate
1 (9.09%)
3 (25.00%)
ECOG
7.11
.029
(0) Fully active
3 (27.27%)
9 (75.00%)
(1) Restricted in physical
strenuous activity
4 (36.36%) 3 (25.00%)
(2) Able to ambulate &
self-care but unable to
perform work activities
4 (36.36%) 0 (0.00%)
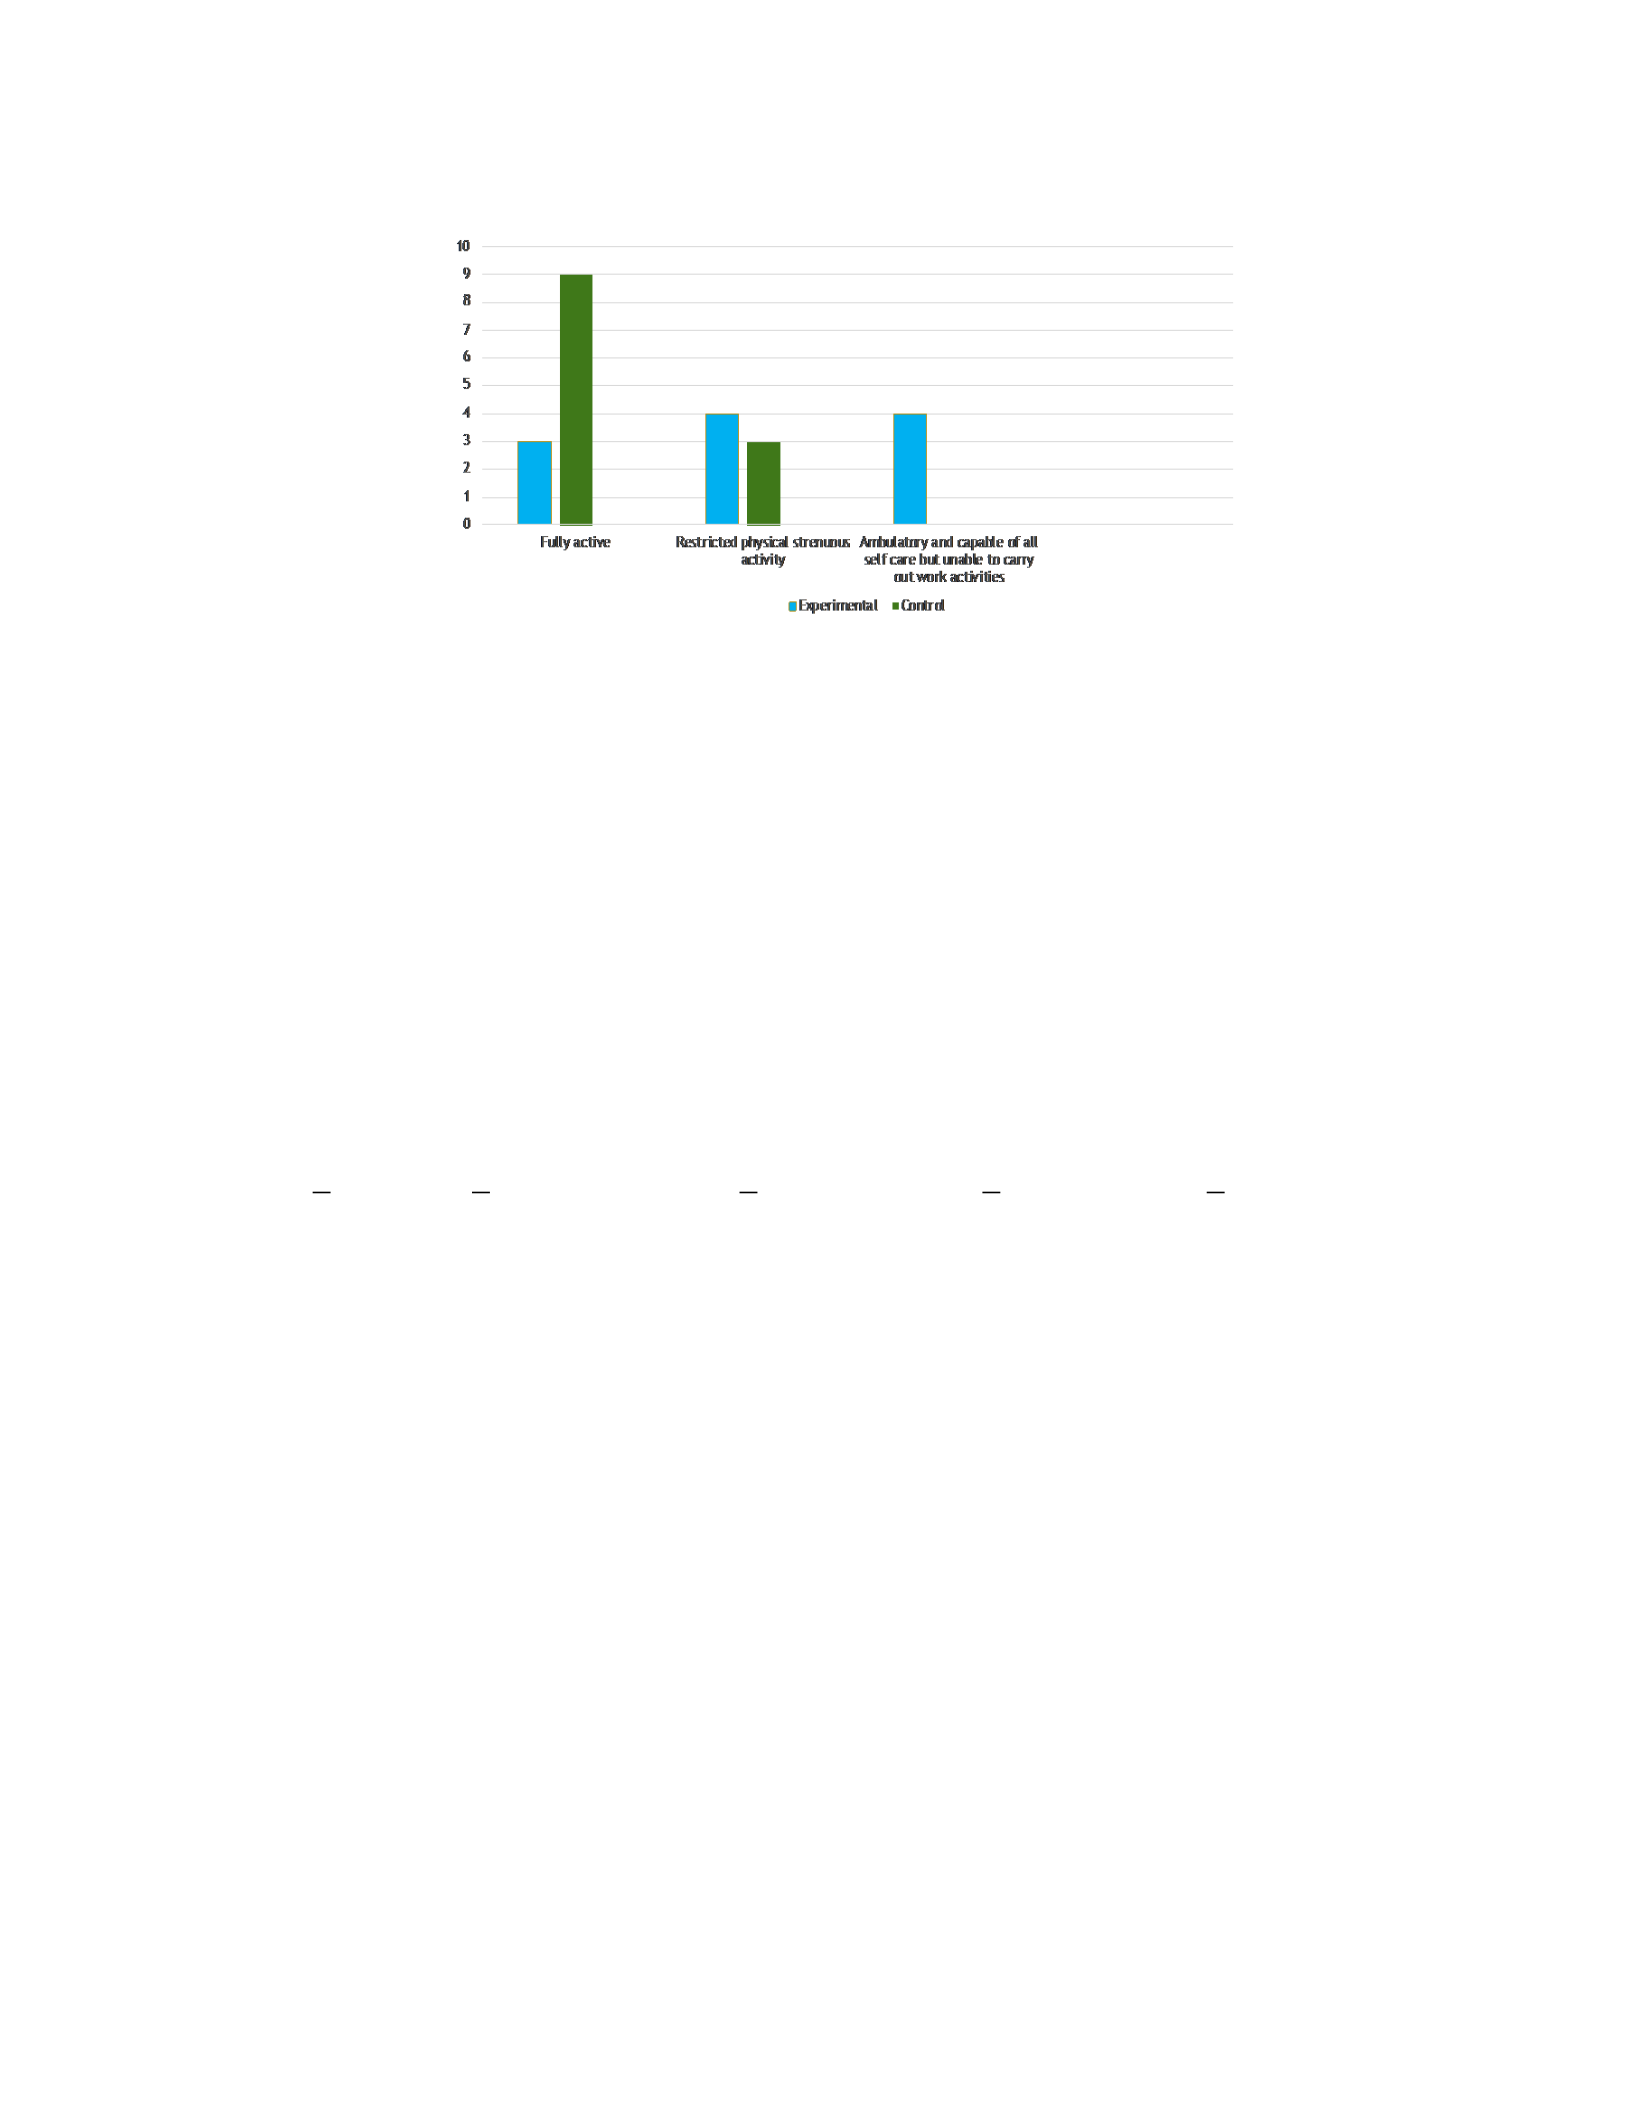
50
Figure 4. Number of participants in both groups for ECOG Scores 0-2.
Cronbach’s Alpha Test of Internal Consistency and Reliability
Composite scores were calculated for hope and QOL through use of the HHI and
OPQOL, respectively. Cronbach’s alpha test of reliability and internal consistency were
evaluated for the two scales. The strength of the alpha values was interpreted through the
guidelines developed by George and Mallery (2020), in which α < .5 Unacceptable,
α > .5 Poor, α > .6 Questionable, α > .7 Acceptable, α > .8 Good, and α > .9 Excellent.
Hope and QOL met the acceptable level of internal consistency (α > .70) for both pre-test
and post-test measurements. This indicated that the participants answered the survey
questions in a consistent manner. Table 3 presents the findings of Cronbach’s alpha test
of reliability.

51
Table 3
Cronbach’s Alpha Test of Reliability
Variable
Number of items
α
Hope
Pre-test
12
.91
Post-test
12
.83
QOL
Pre-test
35
.95
Post-test
35
.92
PICOT Question
How does the implementation of an eight-week hope intervention in seniors 65
years and older who live alone affect their level of hope and quality of life compared to
those levels in seniors 65 years and older who live alone and do not receive the hope
intervention?
In order to address the PICOT question, two independent sample t-tests were first
conducted to analyze for pre-test differences in the level of hope and QOL between the
experimental and control groups. Two additional independent sample t-tests were
conducted to analyze for post-test differences in the level of hope and QOL between the
experimental and control groups. Two mixed model ANOVAs were conducted to assess
for differences in hope and QOL before and after the intervention and between the
experimental and control groups. A mixed model ANOVA is appropriate when analyzing
for differences in a continuous level variable over time and by group (Tabachnick &
Fidell, 2019). Prior to analysis, the assumptions of normality and homogeneity of
variances were tested on the data.

52
Normality Assumption: Shapiro-Wilk Tests
A series of Shapiro-Wilk tests was used to assess the normality assumption. The
normality of assumption reveals that the data falls in a normal distribution, which is an
important factor in using parametric analysis (Mishra et al., 2019). The findings of the
Shapiro-Wilk tests were not statistically significant for hope at post-test (p =.512), and
QOL at pre-test (p = .075) and post-test (p = .822); therefore, the assumption of
normality was supported for these variables. This finding indicates that these variables
approximately follow a bell-shaped distribution, which is one of the assumptions for
parametric analysis. The finding of the Shapiro-Wilk test was statistically significant for
hope at pre-test (p = .017), indicating that the assumption of normality was not supported
for this variable. This finding indicates that the distribution of scores for hope at pre-test
did not resemble a bell-shaped curve. Table 4 presents the findings of the Shapiro-Wilk
tests.
Table 4
Shapiro-Wilk Tests on Hope and QOL (n = 23)
Variable
Shapiro-Wilk Tests
Test Statistic
p
Hope
Pre-test
0.89
.017
Post-test
0.96
.512
QOL
Pre-test
0.92
.075
Post-test
0.98
.822

53
Homogeneity of Variance Assumption:
Levene’s Tests
A series of Levene’s tests was used to assess the homogeneity of variance
assumption, which is one of the assumptions for parametric analysis. Homogeneity of
variances is an assumption in which the population variances of two or more samples are
considered equal. The findings of the Levene’s tests were not statistically significant for
hope at pre-test (p = .499) and post-test (p = .839), and QOL at post-test (p = .513);
therefore, the assumption of homogeneity of variance was supported for these variables.
The finding of the Levene’s test was statistically significant for QOL at pre-test (p =
.042), indicating that the assumption of homogeneity of variance was not supported for
this variable. Due to the assumption of normality not being supported for hope at pre-test
and homogeneity of variance not being supported for QOL at pre-test, a series of non-
parametric Wilcoxon-Signed Rank tests were used as a follow-up to the mixed model
ANOVAs. Table 5 presents the findings of the Levene’s tests.
Table 5
Levene’s Tests on Hope and QOL (n = 23)
Variable
Levene’s Tests
Test Statistic
p
Hope
Pre-test
0.47
.499
Post-test
0.04
.839
QOL
Pre-test
4.69
.042
Post-test
0.44
.513

54
Independent Sample t-tests: Pre-test
Independent sample t-tests were used to examine for pre-test differences between
experimental and control groups. The independent sample t-tests for hope (t = -1.60, p =
.125) and QOL (t = -1.72, p = .100) were not statistically significant, indicating that at
pre-test, there were no significant differences in scores between experimental and control
groups. Table 6 presents the findings of the independent sample t-tests for pre-test hope
and QOL scores.
Table 6
Independent Sample t-tests for Hope and QOL at Pre-test
Variable
Experimental
Control
n
M
SD
n
M
SD
t(21)
p
Hope pre-test
11
37.45
7.24
12
41.50
4.76
-1.60
.125
QOL pre-test
11
114.91
12.17
12
126.25
18.49
-1.72
.100
Independent Sample t-tests: Post-test
Independent sample t-tests were used to examine for post-test differences between
experimental and control groups. The independent sample t-tests for hope (t = -0.51, p =
.618) and QOL (t = -1.34, p = .194) were not statistically significant, indicating that at
post-test there were no significant differences in scores between experimental and control
groups. Table 7 presents the findings of the t-tests for post-test hope and QOL scores.

55
Table 7
Independent Sample t-tests for Hope and QOL at Post-test
Variable
Experimental
Control
n
M
SD
n
M
SD
t(21)
p
Hope post-test
11
40.91
4.39
12
41.83
4.37
-0.51
.618
QOL post-test
11
134.09
15.70
12
142.42
14.04
-1.34
.194
Mixed Model ANOVA: Hope
The findings of the within-subjects effect, time (pre-test vs. post-test), were not
statistically significant, F(1, 21) = 2.50, p = .129, ηp2 = .106, indicating that there were no
significant differences in hope before and after the intervention. Within-subjects is the
pre-test/post-test comparison, so both experimental and control groups were merged for
this comparison. Approximately 10.6% of the variance in hope scores can be explained
by the time factor. For the overall sample (n = 23), mean hope scores before and after the
intervention were 39.57 and 41.39, respectively.
The findings of the between-subjects effect, group membership (experimental vs.
control), were not statistically significant, F(1, 21) = 1.79, p = .195, ηp2 = .079, indicating
that there were no significant differences in hope between experimental and control
groups. Between-subjects looked at group comparison, so all pre-test and post-test were
merged for this comparison. Approximately 7.9% of the variance in hope scores can be
explained by the group factor. The mean hope scores for the experimental and control
groups were 39.18 and 41.67, respectively.
The findings of the interaction effect (time*group) were not statistically
significant, F(1, 21) = 1.70, p = .207, ηp2 = .075, indicating that there were no significant

56
differences in hope by the combination of the time and group. The interaction effect
analyzed pre-test experimental, pre-test control, post-test experimental, and post-test
control. For the experimental group, the mean hope scores before and after the
intervention were 37.45 and 40.91, respectively. Approximately 7.5% of the variance in
hope scores can be explained by the interaction effect, time*group. For the control group,
the mean hope scores before and after the intervention were 41.50 and 41.83,
respectively.
Table 8 presents the results of each effect for the mixed model ANOVA. The
means and standard deviations for hope scores over time and by group are presented in
Table 9. Figure 5 presents a line plot for hope scores over time and by group.
Table 8
Mixed Model ANOVA for Hope Scores by Time and Group
Source
F(1, 21)
p
ηp2
Within-subjects effect (Time: Pre-test vs. Post-test)
2.50
.129
.106
Between-subjects effect (Group: Experimental vs. Control)
1.79
.195
.079
Interaction effect (Time*Group)
1.70
.207
.075
Table 9
Means and Standard Deviations for Hope Scores by Time and Group
Source
Experimental
Control
Total
n
M
SD
N
M
SD
n
M
SD
Hope (Pre-test)
11
37.45
7.24
12
41.50
4.76
23
39.57
6.28
Hope (Post-test)
11
40.91
4.39
12
41.83
4.37
23
41.39
4.30
Total
11
39.18
5.82
12
41.67
4.57
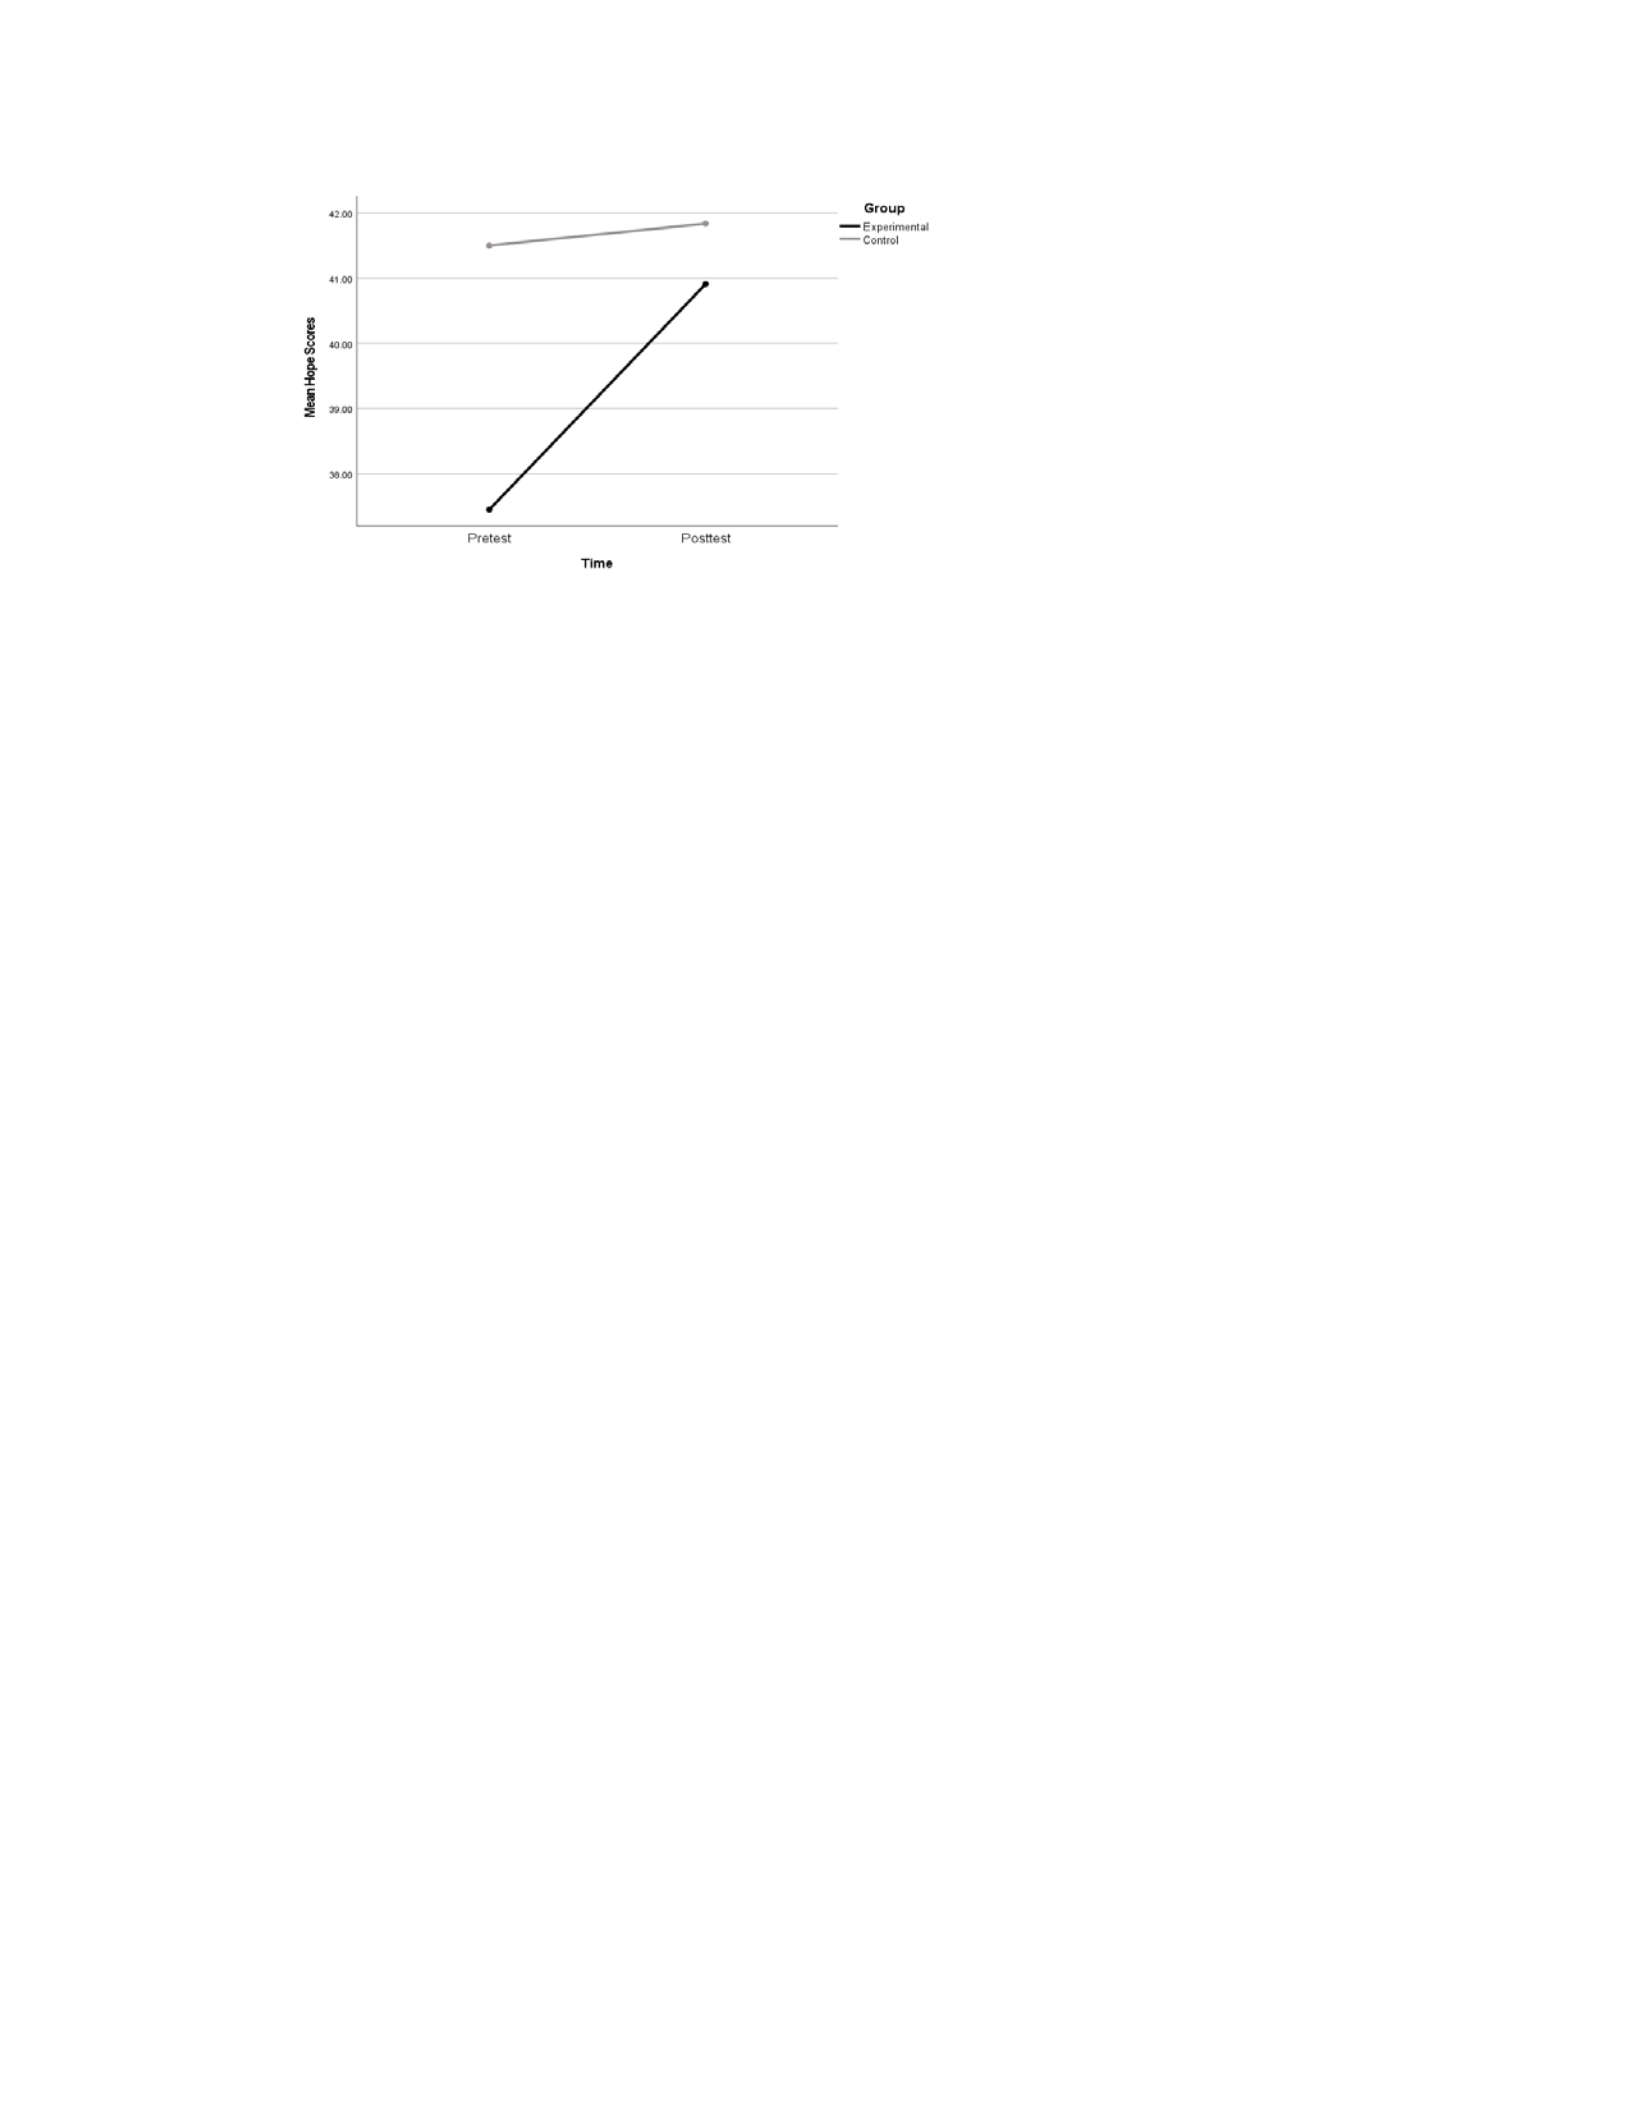
57
Figure 5. Line plot for hope scores over time and by group.
Mixed Model ANOVA: QOL
The findings of the within-subjects effect, time (pre-test vs. post-test), were
statistically significant, F(1, 21) = 105.51, p < .001, partial ηp2 = .834, indicating that
there were significant differences in QOL before and after the intervention.
Approximately 83.4% of the variance in QOL scores can be explained by the time factor.
This finding indicates that for the combined sample (experimental and control group),
there was a significant improvement in QOL. For the overall sample (n = 23), mean QOL
scores before and after the intervention were 120.83 and 138.43, respectively.
The findings of the between-subjects effect, group membership (experimental vs.
control), were not statistically significant, F(1, 21) = 2.55, p = .126, ηp2 = .108, indicating
that there were no significant differences in QOL between experimental and control
groups. Approximately 10.8% of the variance in QOL scores can be explained by the
group factor. The mean QOL scores for the experimental and control groups were 124.50
and 134.34, respectively.
The findings of the interaction effect (time*group) were not statistically
significant, F(1, 21) = 0.77, p = .391, ηp2 = .035, indicating that there were no significant

58
differences in QOL by the combination of the time and group. For the experimental
group, the mean QOL scores before and after the intervention were 114.91 and 134.09,
respectively. Approximately 3.5% of the variance in QOL scores can be explained by the
interaction effect, time*group. For the control group, the mean QOL scores before and
after the intervention were 126.25 and 142.42, QOL scores over time and by group are
presented in Tables 10 and 11. Figure 6 presents a line plot for QOL scores over time and
by group.
Table 10
Mixed Model ANOVA for QOL Scores by Time and Group
Source
F(1, 21)
p
ηp2
Within-subjects effect (Time: Pre-test vs. Post-test)
105.51
<.001
.834
Between-subjects effect (Group: Experimental vs. Control)
2.55
.126
.108
Interaction effect (Time*Group)
0.77
.391
.035
Table 11
Means and Standard Deviations for QOL Scores by Time and Group
Source
Experimental
Control
Total
n
M
SD
n
M
SD
n
M
SD
QOL (Pre-test)
11
114.91
12.17
12
126.25
18.49
23
120.83
16.49
QOL (Post-test)
11
134.09
15.70
12
142.42
14.04
23
138.43
15.12
Total
11
124.50
13.94
12
134.34
16.27
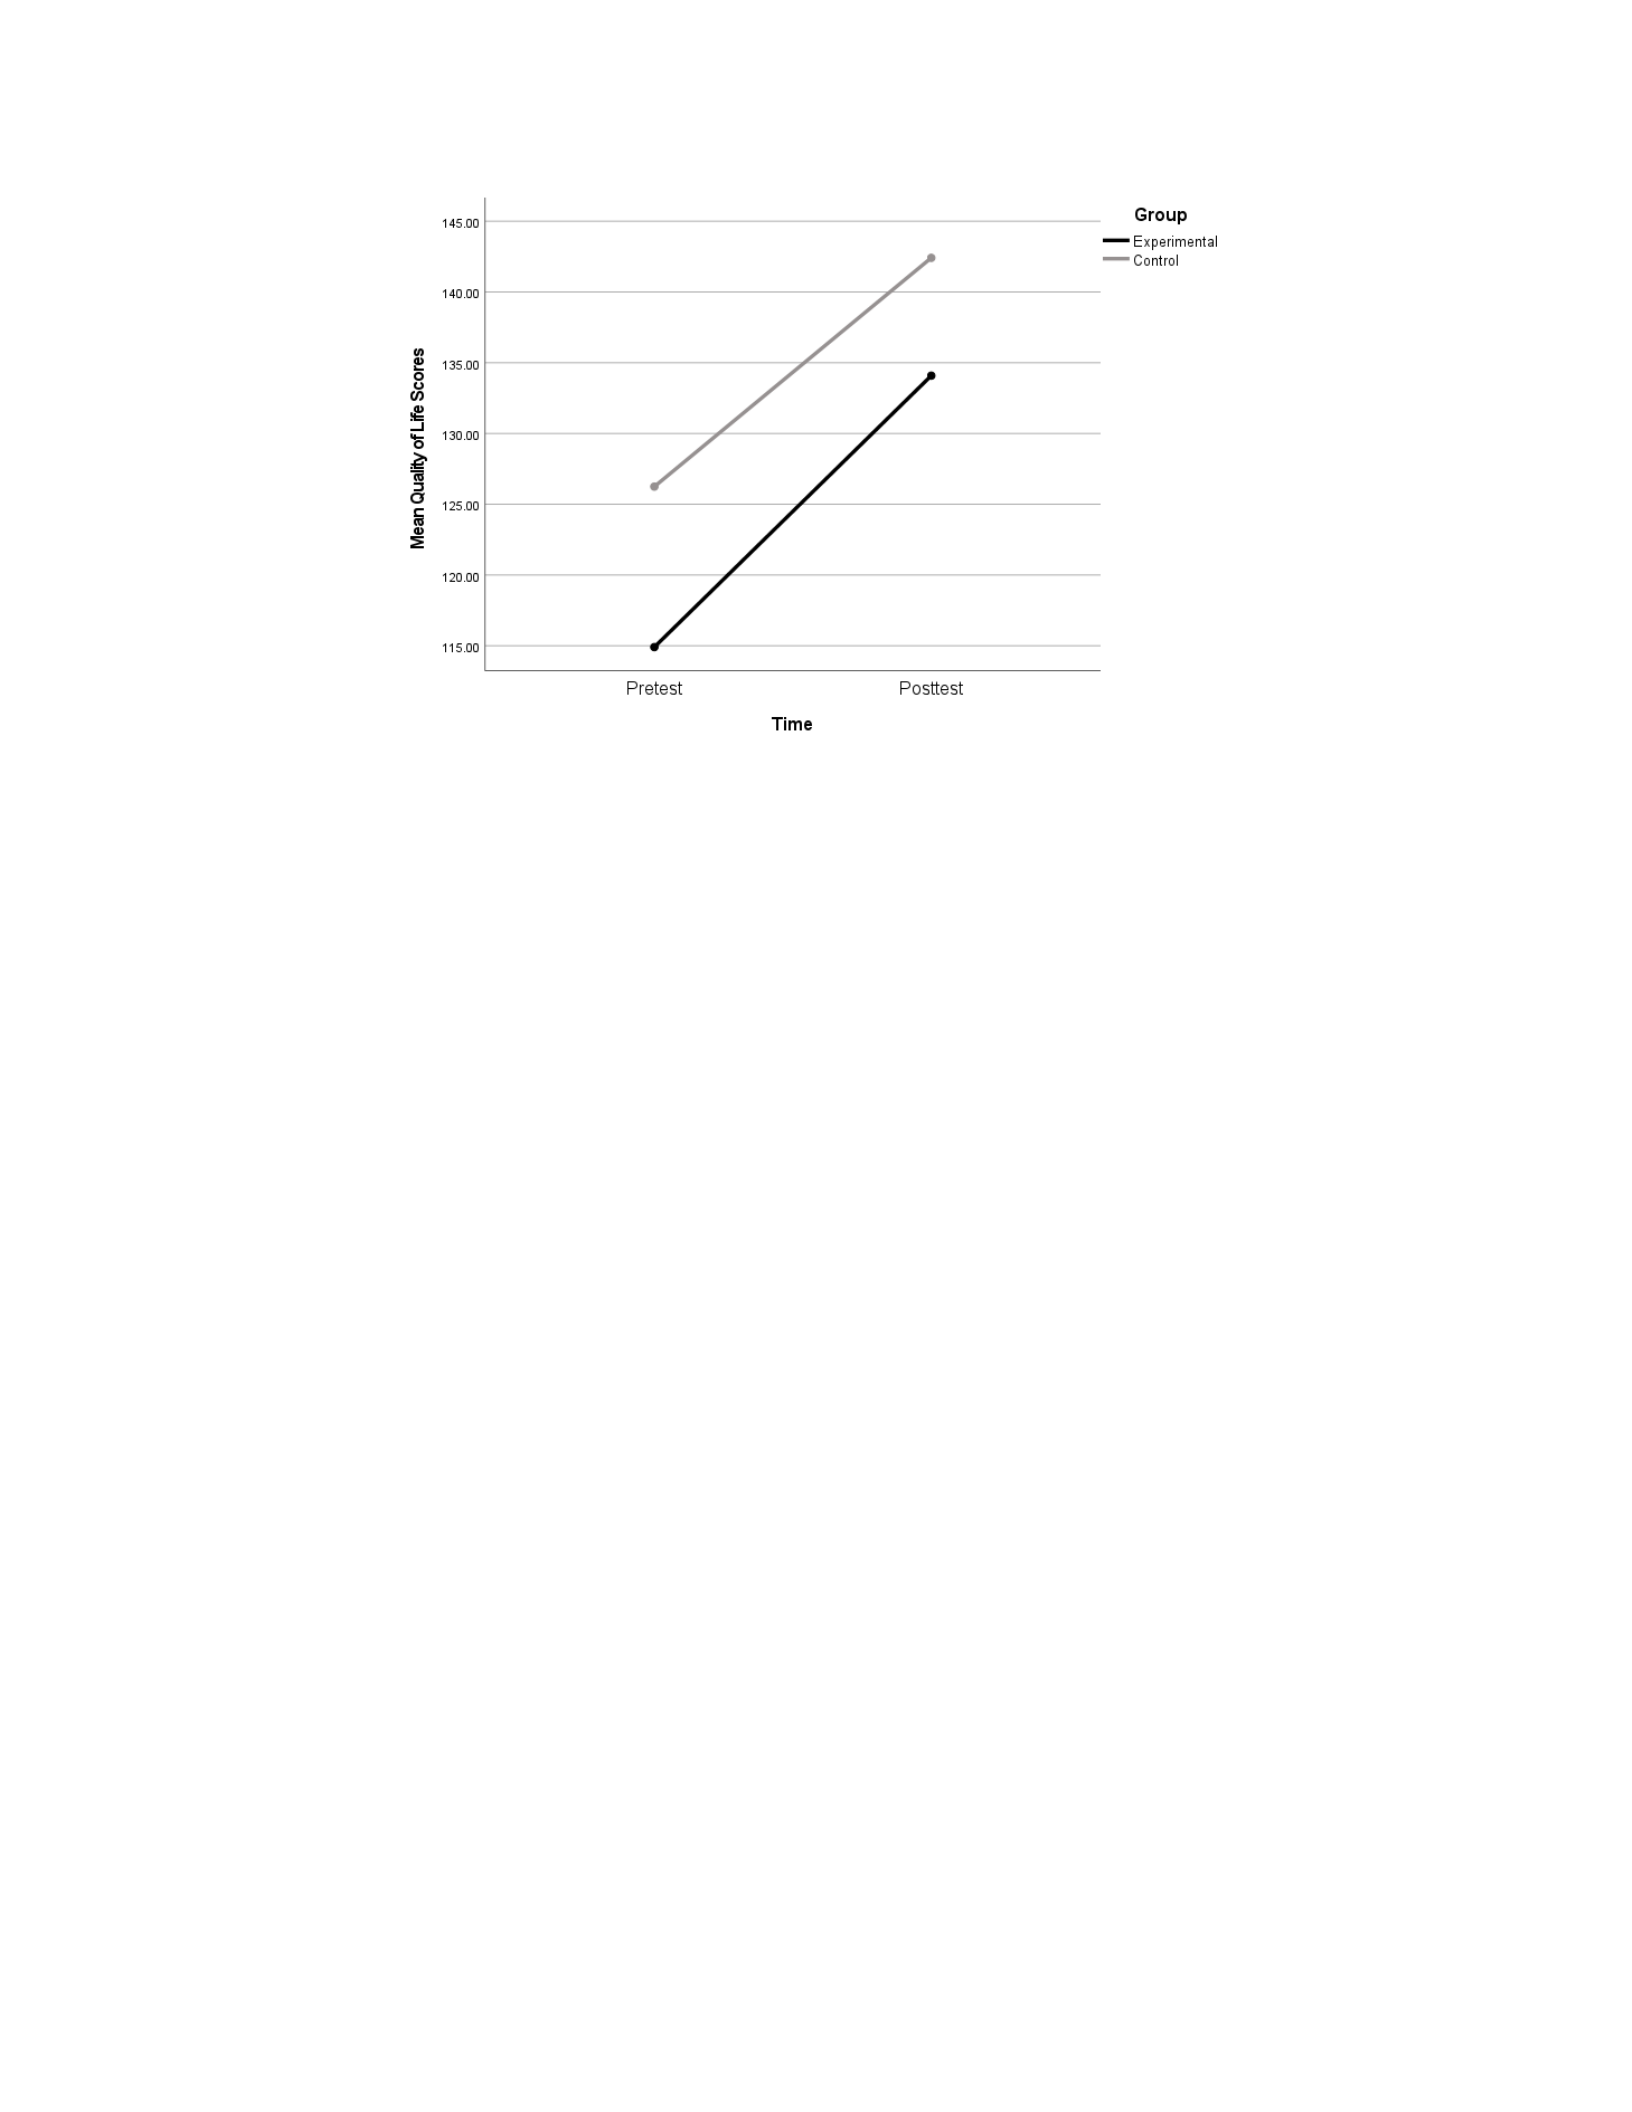
59
Figure 6. Line plot for QOL scores over time and by group.
Wilcoxon-Signed Rank Tests for
Hope and QOL
A series of Wilcoxon-Signed Rank tests was conducted as non-parametric follow-
ups because the assumption of normality and homogeneity of variance assumptions were
not supported, which were essential for parametric analysis. Instead of using the mean to
calculate for the pre- and post-hope level and QOL, a series of Wilcoxon-Signed Rank
Tests used the median to calculate pre-test and post-test hope and QOL. For the
experimental groups, there was a significant improvement in hope (p = .034) and QOL (p
= .003) following the intervention. The control group also demonstrated a significant
increase in QOL. Table 12 presents the findings of the Wilcoxon-Signed rank tests.

60
Table 12
Wilcoxon-Signed Rank Tests for Hope and QOL Before and After Intervention
Source
Pre-test
Post-
test
Median
Median
Wilcoxon-Signed Rank Test Statistic
p
Hope
Experimental
38.00
40.00
-2.12
.034
Control
42.00
42.00
-0.28
.783
QOL
Experimental
113.00
135.00
-2.94
.003
Control
126.50
141.50
-2.99
.003
Ancillary Analysis
Spearman correlations were conducted to analyze the strength of the relationship
between hope and QOL. Spearman correlations were conducted instead of Pearson
correlations because the normality assumption was not supported for hope scores at pre-
test. In addition, homogeneity of variance was not supported for QOL scores at pre-test.
Scatterplots for the relationships at pre-test and post-test are presented in Figures 7 and 8.
Both scatterplots appeared to depict positive associations between hope and QOL.
The finding of the Spearman correlation between hope and QOL at pre-test was
statistically significant (rs = .64, p < .001). The finding of the Spearman correlation
between hope and QOL at post-test was also statistically significant (rs = .74, p < .001).
The correlation coefficients were positive and represented a large effect (r > .50). Table
13 presents the findings of the Spearman correlations.
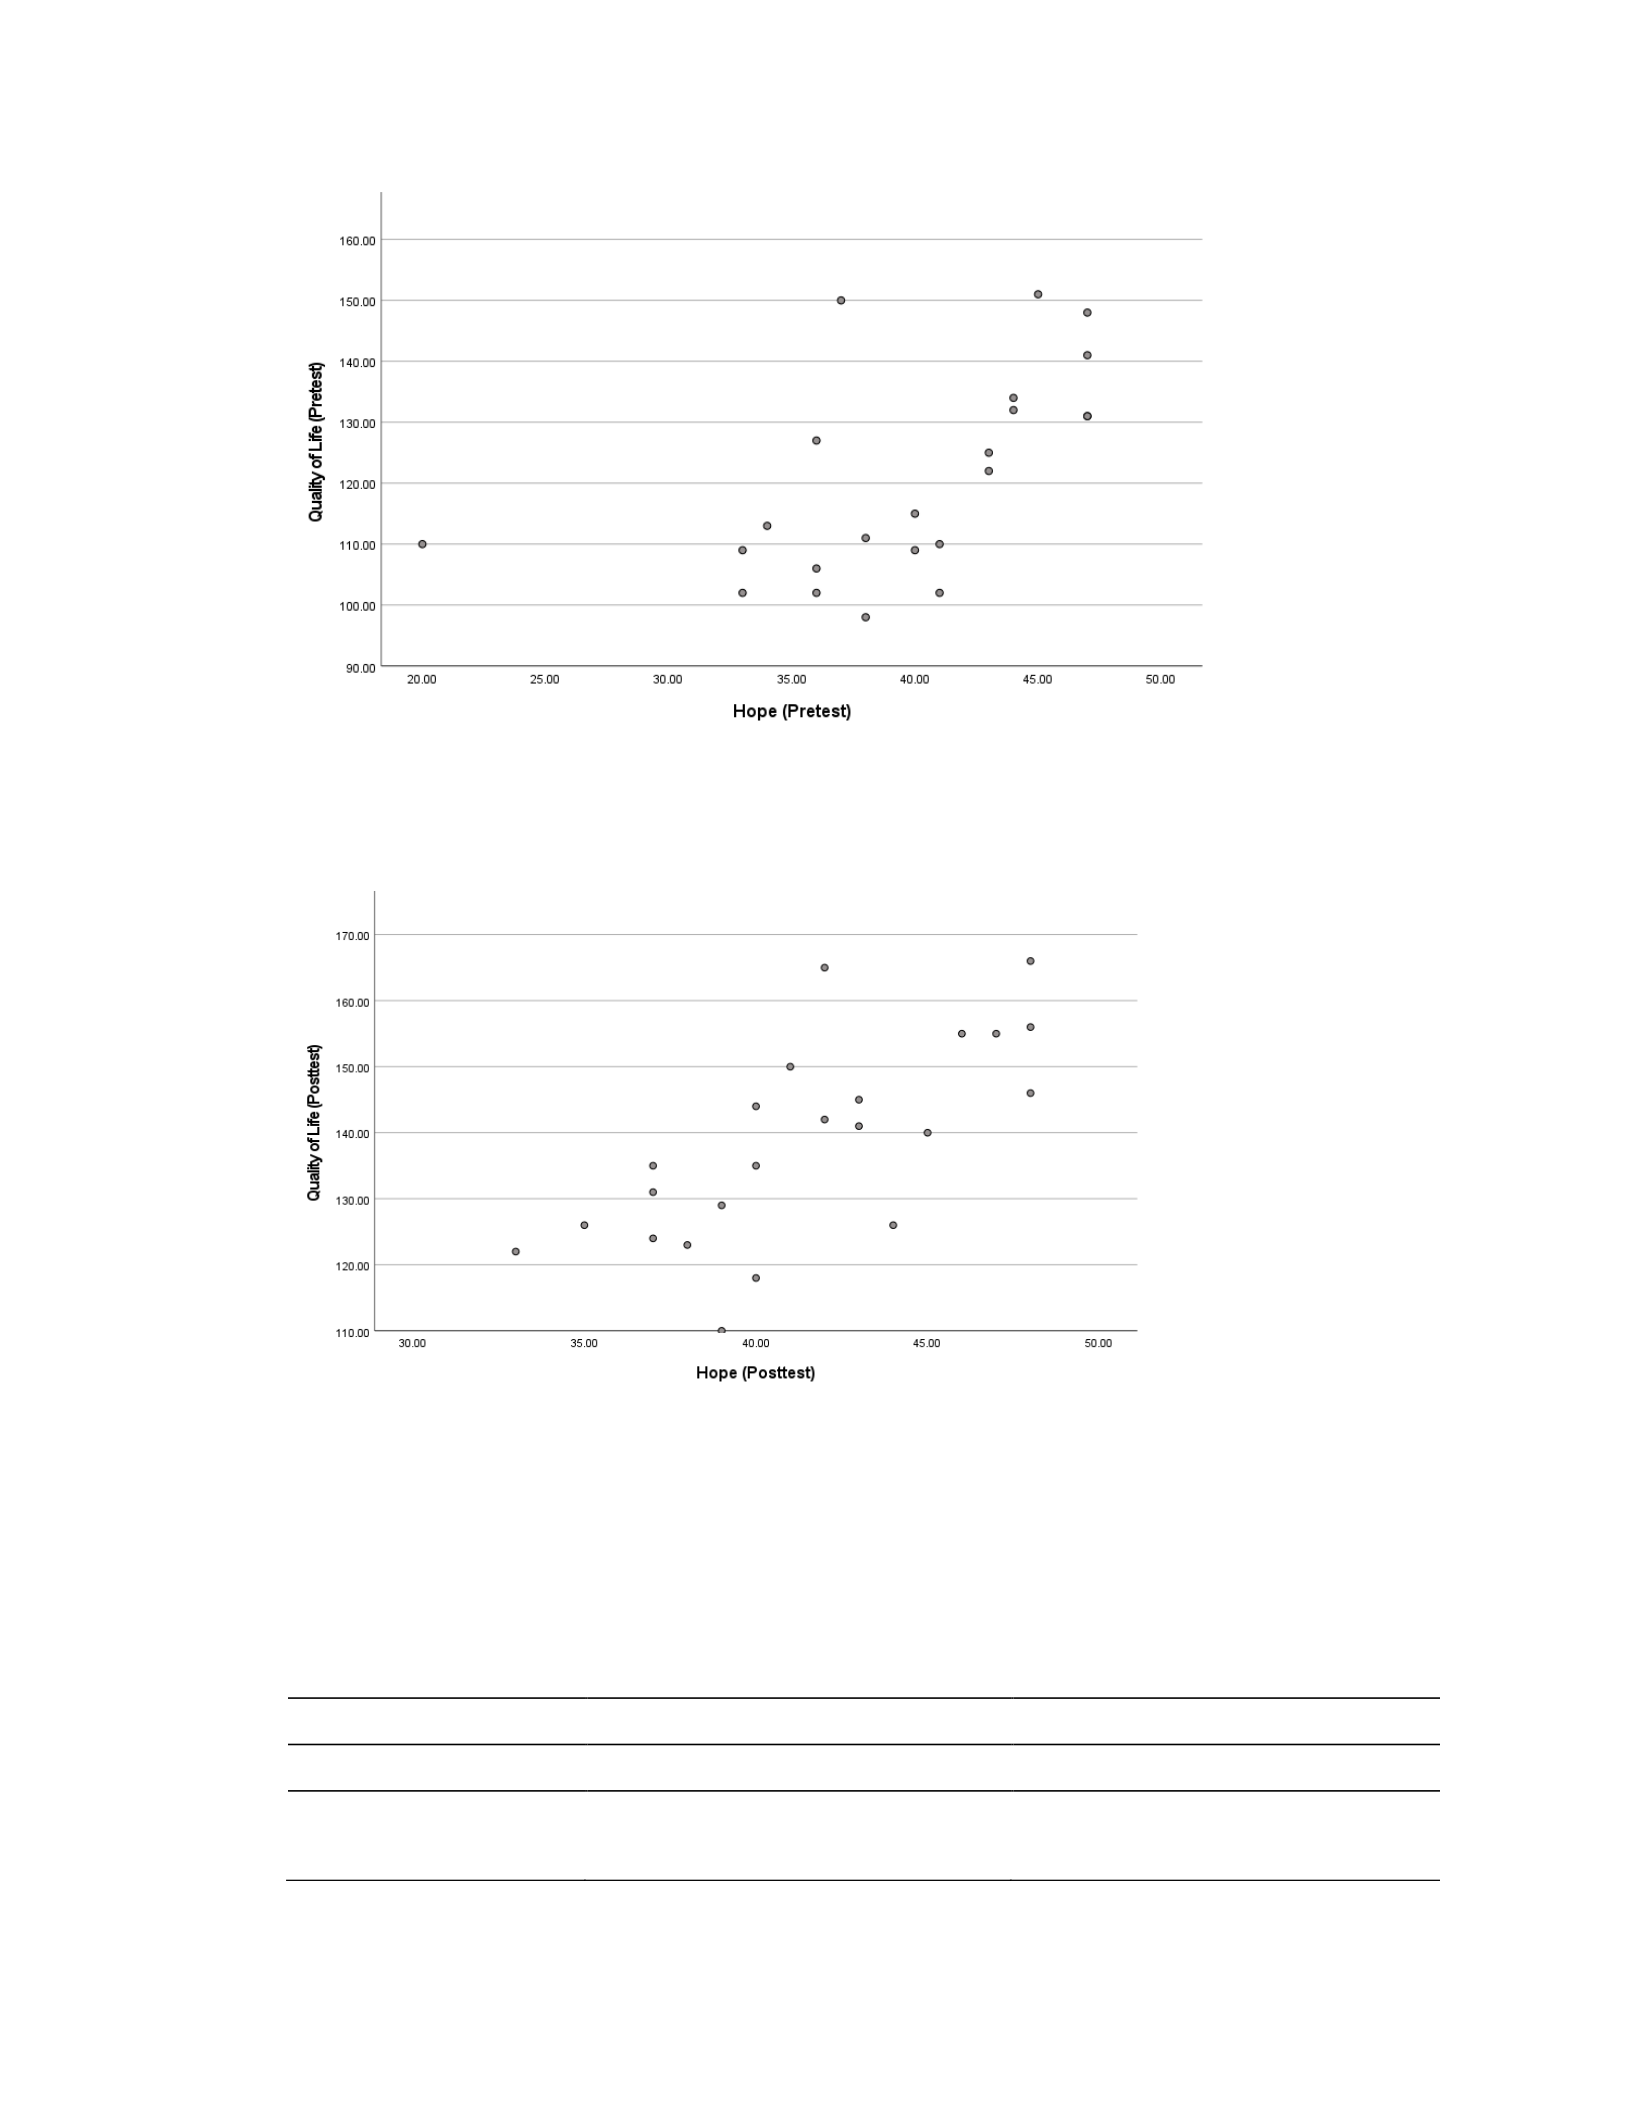
61
Figure 7. Scatterplot between hope and QOL at pre-test.
Figure 8. Scatterplot between hope and QOL at post-test.
Table 13
Spearman Correlations between QOL and Hope
Variable
QOL (pre-test)
QOL (post-test)
rs
rs
Hope (pre-test)
.64*
Hope (post-test)
.74*
*Denotes correlation is significant at .001 level.

62
Summary
The demographic analysis indicated that there were no statistically significant
differences in the demographic variables between the two groups except for ECOG.
Results showed that there was, however, a statistically significant difference between
ECOG and group (p = .029). Independent sample t-tests conducted to examine for pre-
test differences between experimental and control groups showed no statistical
significance for hope (t = -1.60, p = .125) and QOL (t = -1.72, p = .100). Independent
sample t-tests performed to examine for post-test differences between experimental and
control groups indicated no significant differences for hope (t = -0.51, p = .618) and
QOL (t = -1.34, p = .194). Mixed model ANOVA for hope showed no significant
findings. Mean hope scores for the experimental group before and after the interventions
were 37.45 and 40.91, respectively, indicating that there was some increase in hope level
in the experimental group before and after the intervention, but it was not statistically
significant. Mixed model ANOVA for QOL indicated that there were significant
differences in both groups before and after the intervention F(1, 21) = 105.51, p < .001.
Wilcoxon-Signed Rank tests conducted as back-up for the parametric revealed that there
was a significant improvement in hope (p = .034) and QOL (p = .003) following the
intervention. Spearman correlations conducted to analyze the strength of the relationship
between hope and QOL depicted positive associations between hope and QOL.

63
CHAPTER 5
DISCUSSION
There is now an increasing senior population across the world. This will soon
surpass that of children, thus leading to a majority that is old or very old (Zarghami et al.,
2018). Studies indicate that the number of elderly people living alone continues to grow
(Ng et al., 2015). Living alone has also shown to affect the wellbeing of the elderly
population, impacting their hope and QOL (Gupta & Singh, 2020; Hwang et al., 2020;
Yeh & Lo, 2004).
The main objective of this project was to determine whether an 8-week Hope
Intervention Program would improve the levels of hope and QOL in elderly people who
lived alone. This chapter includes discussion of the major findings of the study and their
relationship to the objectives and the theoretical framework. In addition, the chapter
includes discussions of the project’s significance and its impact on future nursing practice
and nursing research. Furthermore, study strengths, limitations, and plans for
dissemination are described, as well as how the project relates to the Doctor of Nursing
Practice (DNP) Essentials as defined by the American Association of Colleges of
Nursing ([AACN], 2006).
Summary of Study Findings
The purpose of this project was to evaluate the effects of a non-pharmacological

64
intervention, in this case, the use of HIP on hope and on the QOL in senior individuals
who live alone. To the project manager’s knowledge, this study was the first which
utilized HIP to explore the levels of hope and QOL in the elderly population.
Participants’ Demographics
The population for this project was drawn from the general community in
Southwest Michigan. Thirty-one individuals from Southwest Michigan originally signed
the informed consent to participate in the study. A final total of 23 participants completed
the study—11 participants in the experimental group and 12 participants in the control
group.
There were no statistically significant differences pertaining to demographic
variables between the experimental and control groups except for ECOG scores. It was
observed that the majority participants in the study were white. There was one black
participant in the experimental group and one in the control group, and no Hispanics
represented in the study. There was an under-representation of male participants in the
study—they were all female except for one male participant. These findings are
consistent with Berrien County demographics. According to the U.S. Census Bureau
(2021), Berrien County Demographics Summary showed that the largest Berrien County
racial/ethnic groups are White 79.9% followed by Black 14.4% and Hispanic 6.1%. U.S.
Census Bureau also indicated that the Berrien County, Michigan Gender Ratio was
50.7% females to 49.3% male. There was no statistically significant difference in the
marital status or education level between both groups. The study recruited participants
based on whether their age was 65 or higher. Therefore, no age range data was available.
The ECOG score was statistically significant between the two groups. It showed

65
that more participants in the experimental group reported restricted activity levels
compared to the control group. A total of four (36.36%) participants in the experimental
group reported that they were able to ambulate and do self-care, but were unable to carry
out work activity, while none in the control group reported that they were restricted with
work activities. While three (27.27%) participants in the experimental group said they
were fully active, nine (75%) participants in the control group reported that they were
fully active. These factors may have influenced the final results since individuals who
remain active tend to have a positive outlook towards life (Lucas et al., 2019).
Hope Level Analysis
The HHI survey was utilized to assess the baseline for the level of hope for both
the experimental and control groups. The survey was completed by both groups at the
end of the eight weeks. Independent sample t-tests conducted to examine for pre-test
differences between the experimental and control groups showed no statistical
significance for pre-test hope (t = -1.60, p = .125). The results also indicated that the
independent sample t-tests for post-test hope (t = -0.51, p = .618) was not statistically
significant. This showed that there was no significant difference on the level of hope after
the HIP intervention between the experimental and control groups.
Zareei Mahmoodabadi et al. (2019) indicated that the hope therapy program
conducted on 24 elderly women showed a statistically significant difference in the level
of hope before and after the intervention in the study group. According to Herth (2001),
HIP positively influenced in rebuilding and maintaining hopeful veneer in 38 participants
with first-time recurrent cancer who were receiving cancer treatment. Hence, it was
expected that hope interventions would reveal a similar effect in the current study.

66
The findings in the current research led me to identify that other variables may
have had an impact on the results such as sample size, ECOG scores, and social
desirability bias. The project manager noted sample size and how it may have played a
role influencing the results as one of the variables. The assumption of normality was not
supported for the hope variable at pre-test as indicated by the Shapiro-Wilk test, which
showed a statistical significance for hope at pre-test (p = .017), meaning the collected
data for hope at pre-test did not resemble a normal distribution, which was essential for
parametric analysis. The literature indicates that as the sample size decreases, sufficient
power is not guaranteed to affect the results. To confirm the power in the normality test,
it is essential to obtain an adequate sample (Kim & Park 2019). Howell (2013) revealed
that when the sample size is greater than 50 cases, violations of normality are not
problematic. Thus, 50 cases is the target where normality violations are not problematic.
The sample size was a limitation for all analyses. This situation may play a role in
influencing the post-hope level as not being significant between experimental and control
groups despite the HIP intervention in the experimental group.
The project manager observed another variable that may have influenced the
findings—ECOG scores between both groups. The current study finding of the chi-square
test between ECOG and group was statistically significant, χ2(2) = 7.11, p = .029. The
current study experimental group had a greater level of impairment reflected by ECOG
scores, compared to the control group (see Table 2), indicating that the participants in the
control group were more active with better ability to care for themselves than the
participants in the experimental group. The significant difference on ECOG between
groups may contribute to the insignificance in the pre- and post-hope level.

67
The project manager also noted that social desirability bias in the self-reported
surveys could have influenced the results. Some participants in the experimental group
said during some of the sessions that they may have reported high scores for the pre-tests
because they did not want to be seen as less hopeful in life, thereby answering in ways
that put them in a more positive light, rather than answering honestly. Social desirability
bias refers to the research participants’ tendency to select responses that they believe are
more socially desirable or acceptable rather than selecting responses that reflect true
feelings and thoughts (Krumpal, 2013). The literature shows that selecting appropriate
data collection strategies that can reduce respondents’ uneasiness when answering a
sensitive question may minimize this bias and generate more valid data (Krumpal, 2013).
Strategies such as techniques to introduce the study, asking questions, establishing
rapport, collecting data in an environment that allows for privacy, and, when possible,
collecting data through mail surveys rather than face-to-face or telephone interviews have
shown to reduce the social desirability bias (Bergen & Labonté, 2020). The current
participants voiced social desirability bias may have influenced the results.
In addition, current study findings showed that the mean hope score at pre-test for
the experimental group was lower (37.45) compared to the hope scores at pre-test for the
control group (41.50), indicating that the difference in hope already existed between the
two groups. Therefore, the significant differences on hope level before the intervention
indicated that the hope level was not equally distributed between two groups. This
unequal distribution on pretest hope may contribute to the insignificant results after the
intervention for the participants between two groups. In addition, participants in the
experimental group received 8 weeks HIP, and participants in the control group might

68
also have gone to the wellness clinic and senior center for individual visits. Therefore, the
hope level may also have improved in the control group after 8 weeks, resulting in the
insignificance of posttest hope between the two groups.
QOL Level Analysis
The current study results also revealed that the independent sample t-tests for
QOL were not statistically significant at pre-test (t = -1.72, p = .100) and post-test (t = -
1.34, p = .194), indicating no significant differences at post-test in scores between
experimental and control groups. In the previous literature, improved perception and
understanding of hope through hope intervention has shown to increase the QOL among
the elderly (Zareei Mahmoodabadi et al., 2019). Another study conducted by Binaei et al.
(2016) showed that hope-promoting strategies were beneficial in improving the QOL in
people with chronic conditions. The current study results did not reflect the previous
study findings. As noted with hope level results analysis, other variables such as smaller
sample size, ECOG scores, and social desirability bias may have contributed to the result
of no statistically significant differences with QOL before and after the interventions.
The finding of the Levene’s test was statistically significant for QOL at pre-test (p
= .042), indicating that the assumption of homogeneity of variance was not supported for
this variable plays a role influencing the post QOL result. This may contribute to the
QOL as not significant in post-test. Homogeneity of variance, which is essential for both
t-tests and F tests analysis, refers to the assumption in which the population variances of
two or more samples are considered equal. The literature shows that the smaller sample
size greatly influences the values of individual samples on variance. As the sample size
increases, this variability becomes stable (Kim & Park 2019; Uttley, 2019)

69
Even though the independent sample t-tests for QOL were not statistically
significant, a mixed model ANOVA for QOL within-subjects effect showed statistically
significant differences, indicating that there were significant differences in QOL before
and after the intervention for all participants in both the experimental and control groups.
Therefore, some of the reasons may be because participants in the experimental group
received 8 weeks HIP and participants in control group might also have gone to the
wellness clinic and senior center for individual visits. Therefore, the QOL were all
improved in all participants due to socialization and human interactions.
Hope and QOL
Even though the independent sample t-tests for hope were not statistically
significant, the mixed model ANOVA showed that the mean hope scores in the
experimental group was increased from 37.45 (pre-hope) to 40.91 (post-hope) in the
experimental group as compared to the control group—41.50 (pre-hope) to 41.83 (post-
hope; see Table 9). The line plot for hope scores revealed a positive impact on the
experimental group as noted in Figure 5. Instead of using the mean to calculate for the
pre- and post-hope level, a series of Wilcoxon-Signed Rank Tests used the median to
calculate pre-test and post-test hope. The findings indicated that there was a significant
improvement in hope (p=0.034) after the intervention (see Table 12). This result showed
that HIP had a positive impact on hope perception in participants in the experimental
group.
Even though the independent t-tests did not indicate significant improvement in
QOL, the mixed model ANOVA for the pre- and post-QOL score of within-subject for all
participants was significantly different. In other words, the QOL scores were improved

70
for all participants in both the experimental and control group. The QOL score increased
from 114.91 to 134.09 in the experimental group. The QOL score also increased from
126.25 to 142.42 in the control group (see Table 11). In the line plot, improvement was
indicated in both groups (see Figure 6). A series of Wilcoxon-Signed Rank Tests used the
median instead of the mean to calculate pre-test and post-test QOL. It indicated that there
was a significant improvement in QOL in both experimental (p=0.003) and control
(p=0.003) groups (see Table 12). This result showed that HIP had a positive impact on
QOL perception in participants in the experimental group. However, for the participants
in the control group, their improvement in QOL may be because of the frequent visits to
the wellness clinic for their own purpose or people interactions in the wellness clinic, as
well. Still, for the participants in the experimental group, HIP may have had a positive
influence on the QOL outcome.
The study results showed positive associations between hope and QOL as noted in
Figures 7 and 8. Hope is an essential factor that strengthens both physiological and
psychological defenses leading to an improved level of QOL (Herth, 2001). Studies
indicated that there is a positive relationship between the level of hope and QOL
(Alshraifeen et al., 2020; Shen et al., 2020).
In the United States, there is an increasing number of senior individuals who live
alone and present adverse health effects associated with aging (Marcus-Varwijk et al.,
2019). Sickness is a disease condition that can affect body, mind, and spirit. Hope plays a
crucial part with coping and healing. Studies indicate that hope interventions can benefit
individuals by rebuilding and maintaining a hopeful outlook towards life (Chi, 2007;
Herth, 2001; Salamanca-Balen et al., 2021). The results of the current study are

71
consistent with the literature findings that there are positive associations between hope
and QOL.
Implications for Practice
Evidence-based approaches are essential in nursing practice to provide quality
care through improved education and treatment modalities. This was designed to examine
whether elderly people who live alone could benefit from the Hope Intervention Program.
Betty Neuman’s systems model which holds that individuals should be treated
holistically, provided the theoretical underpinning for this study.
Neuman viewed the person as an open system with physiological, developmental,
sociocultural, psychological, and spiritual variables. The system is protected by a series
of concentric rings. Stressors, which may be interpersonal or environmental, have the
potential of penetrating the normal line of defense when it offers inadequate protection
and disturb the wellness of the client (Alligood, 2018). Interventions should focus on the
relief of and protection from stressors (Butts & Rich, 2015; de Almeida et al., 2018). The
Hope Intervention Program consisted of interventions that incorporated education and
activities to address the four attributes of hope to meet and improve the social, emotional,
spiritual, and rational needs of patients, ideally leading to an increased level of hope and
improved QOL (Herth, 2001).
Current findings showed that individuals who participated in the program showed
some improvement in their levels of hope and QOL according to A Line Plot (Figures 5
and 6) and Wilcoxon-Signed Rank tests (Table 12), even though they were not
statistically significant according to the independent t-tests (Tables 6 and 7). This points
to the observation that HIP led to some positive trending in improving hope and QOL

72
levels. Because hope and QOL are multidimensional (Soósová, 2016), nurses may need
to collaborate with other healthcare professionals to treat the individual as a whole
person. Approaches that focus on empathy, encouragement, interactions with family and
friends, appreciation for nature, involvement in the community activities, and gratitude,
for example, are shown to be effective in improving hope and QOL in seniors living
alone (Herth, 2001).
The HIP could be incorporated in the curriculum for health professionals as one
of the interventions to increase hope and QOL in elderly people. School systems could
work with local senior centers and local governmental agencies to connect students with
seniors in local communities and develop a buddy system where students can interact
with seniors regularly to improve their outlook toward life and have a positive impact on
the community.
Project Strengths
There were not many studies done on seniors living alone regarding this topic and
HIP. This project sought to fill the needs of the growing elderly population who live
alone in order to improve the levels of hope and QOL by utilizing the HIP. In addition,
the study utilized an in-person hope intervention in a very special period which was
during the COVID pandemic. During that time, seniors who lived alone needed to have
support to improve their hope and QOL not only for the loneliness but also for the
pandemic “isolation” on human interaction. Therefore, the project timing was a strength.
For the HIP evaluation, participants in the experimental group were asked to
evaluate the HIP by responding to 16 questions. They were asked to rate the HIP sessions
and the exercise activities included in the HIP on a scale of 1 (Most helpful) to 5 (Not

73
helpful at all) (see Appendix K). All the participants in the experimental group completed
the evaluation. The participants’ overall evaluation of the HIP was positive. The key
findings were that 45.5% rated HIP as “most helpful” and 54.5% rated it as “helpful.” No
one rated HIP as not helpful. One participant commented that the “sessions truly blessed
me. Include me in the next program.” Another participant commented that the “classes
were wonderful. I wish there was another class.”
Project Limitations
Project limitations included sample size, accessibility of the program, length of
the program, and self-reported data. The power analysis indicated that a minimum of 17
participants was required in each group. In the current study, even though the
experimental group started with 16 participants at the beginning of the HIP intervention,
it ended with 11 participants for the final analysis. Even though the data showed a
statistical insignificance for hope after the HIP, the HIP interventions had some positive
effect on the hope and QOL levels as indicated by the non-parametric tests. Mixed model
ANOVA within-subject effects indicated statistical significance for both groups for QOL.
Therefore, a larger sample size may be needed to increase study power and statistical
certainty.
The project manager also identified the fact that the length of the program was a
limitation. During the recruitment, many individuals said that if the program had been for
4-6 weeks, they would have participated in the study. Some individuals also said that if
the HIP was offered through online sessions or even as one-on-one sessions, they would
have felt comfortable participating. Future studies can be conducted to assess the HIP
effects on these variables.

74
Implications
Hope intervention has the potential of enhancing hope and QOL in elderly people.
The data suggested that people experienced an increase in their hope levels, thus
positively impacting QOL. The findings indicate that the current study positively
influenced the participants who received interventions. The current study findings may
add to professionals’ knowledge about hope and its effect on hope and QOL in seniors,
especially those who live alone.
The HIP instructions were safe, easy to follow, and were an inexpensive way to
enhance hope and QOL in participants. Professionals may consider all or some of the
aspects of the HIP as a part of their care plan to help others live a hopeful and quality life.
Approaches that focus on empathy, encouragement, appreciation for nature, and gratitude
which were part of the HIP were shown to be effective in improving hope and QOL in
seniors living alone. Nurses should be aware of these intervention approaches to improve
hope and QOL in seniors living alone. Study findings may increase interest in other
professionals to conduct future studies including multiple sites for recruitment to obtain
larger sample size that would allow for more data points, increase the power of the study.
Future studies may compare the effects of HIP between individuals who have been cared
for either an assisted living facility or at home.
Plan for Dissemination
This study will be sent to ProQuest for publication following the approval of the
associated departments of Andrews University in order to expand the distribution of the
study findings. A PowerPoint presentation of the study results will be shared at the local
home health agency and senior centers. The purpose is to encourage and educate nurses

75
caring for the elderly to adapt the HIP and perhaps seek other approaches for their
sessions as they meet with clients. The project findings will also be presented via poster
presentation or oral presentations at nursing conferences or interdisciplinary conferences.
A manuscript will be prepared for publication.
Recommendations
According to the study findings, five recommendations are suggested:
• A similar study can be replicated using a larger sample size to increase
statistical power.
• A similar study can be conducted to utilize online hope intervention.
• A study could be conducted to investigate the effectiveness of hope
intervention between group therapy and one-on-one therapy.
• A study could be conducted to investigate the effectiveness of hope
intervention between in-person and on-line therapy.
• This project can be applied to elderly individuals living in assisted living
settings.
Use of the DNP Essentials
The doctor of nursing practice (DNP) degree was developed as a response to the
complex demands and changes in health care. The project was guided by Essentials for
Doctoral Education for Advanced Nursing practice, which are the foundational
competencies for an advance practice role (AACN, 2006). Seven of the eight Essentials
were utilized (I, II, III, IV, VI, VII, and VIII).

76
Essential I: Scientific Underpinnings for Practice
Essential I: Scientific Underpinnings for Practice addresses the scientific
foundation of nursing and the importance of integrating the science of nursing with
mastery from human physiology, psychology, as well as ethics and organizational
sciences in order to offer the most advanced practices in nursing (Chism, 2109). The
project manager recognized the importance of wholeness of health in individuals and
their continued interaction with their surroundings. Working among the elderly
population, the project manager identified the factors that were affecting their wellbeing.
Feelings of loneliness, pain, depression, anxiety, powerlessness, and hopelessness were
some of the identified components affecting the QOL in this population. This recognition
along with literature review on QOL and interventions to improve QOL led me to the
study topic. This project utilized a systems model theory by Betty Neuman, along with
education and hope intervention to seniors living alone to alleviate the feelings of
loneliness and improve their hope and QOL levels. The project manager was mindful of
the ethics concepts and obtained IRB approval and followed IRB protocol.
Essential II: Organizational and Systems Leadership
for Quality Improvement and Systems Thinking
Essential II involves recognizing and assessing the needs of people, communities,
and institutions. Conceptualizing new practice models that are founded on nursing
science to address the present and future demands of the people is a distinguished aspect
of DNP graduates (AACN, 2006). The current study was developed and implemented
during COVID 19 challenging times. Essential II assisted the project manager to be
keenly aware of the dynamics between organizational processes and their impact on

77
health care providers’ policy changes and the potential effects on those who are receiving
care. As an agent of change, it allowed me to research and explore alternative ways, in
this case, the HIP, in order to reach the identified population to improve hope and QOL in
this population. The project manager plans to share the findings with managers and other
professionals in order to implement HIP as one of the quality improvement measures for
improving QOL in the elderly population.
Essential III: Clinical Scholarship and Analytical
Methods for Evidence-Based Practice
Essential III: Clinical Scholarly and Analytical Methods for Evidence-Based
Practice (EBP) focuses on DNP’s role of combining clinical experience with scientific
research and then translating it into practice, thus enforcing the relationship between
science and practice (AACN, 2006). Evidence-based practice that is strengthened by
solid research and clinical skill, is central to modern health care. The DNP is poised to
play a critical role in its development. As a clinical manager, working in the Home
Health industry, the project manager noted that COVID isolation worsened the overall
health of those individuals who lived alone in the communities, as well as those who
lived in assisted living facilities and yet felt lonely and depressed due to confinement to
their rooms. This phenomenon led to reduced healthcare services and a decline in their
physical, emotional, and social conditions. This project sought to improve hope and QOL
for seniors who lived alone, as well as to evaluate the HIP for uses for future purposes in
this identified population in order to deliver evidence-based quality care within the
assisted living settings, organizations, and communities.

78
Essential IV: Information Systems-Technology and Patient-
Care Technology for the Improvement and
Transformation of Healthcare
Understanding the importance of Essential IV assisted me to communicate
effectively with the participants and deliver the interventions during this project though
the utilization of information systems/technology. The literature is clear that proficiency
in information technology is essential in promoting the use of evidence-based practices
(Chism, 2019). The project manager investigated and accessed the instruments (HIP and
other screening tools), implemented and evaluated the project through these systems in
order to address identified issues and improve quality care (Zaccagnini & White, 2017).
The project manager utilized text messaging to communicate with the participants as
needed and delivered some of the interventions via PowerPoint presentation, making the
sessions more meaningful and productive. Statistical analysis was conducted through
SPSS. The project manager was successful in completing this study effectively with the
help of information systems/technology.
Essential VI: Interprofessional Collaboration for Improving
Patient and Population Health Outcomes
Essential VI focuses on facilitating and team building aspects of the DNP’s role.
Interprofessional collaboration has become an integral part of decision-making with
healthcare delivery (Chism, 2109). Working in collaboration with other committee
members, the project manager was able to plan, implement, and evaluate this project
successfully. Team members consisted of the project chair, a chiropractor, and a
statistician. The team members assisted with needed guidance to complete the project.
The project manager developed the recruitment flyer in collaboration with the chair and

79
another committee member and distributed it in the local wellness clinics, communities,
churches, and senior centers. The project manager visited the local senior centers and
contacted seniors at the wellness clinics to recruit for the study. The project manager
communicated the study details in person and via phone with potential participants in
order to build interest in participating in the study. The project manager was successful in
generating interest in the local wellness clinics and elderly population in order to
understand the factors affecting the QOL in the elderly and the strategies for improving
QOL in the elderly who live alone.
Essential VII: Clinical Prevention and Population
Health for Improving the Nation’s Health
This Essential expects the DNP graduates to identify gaps in the healthcare
system and develop programs for health promotion and risk-reduction in order to impact
the health status of people in multiple settings (AACN, 2006). The project manager
achieved these goals by identifying the gap in the literature regarding elderly people
living alone and by implementing interventions through HIP to increase their awareness
of hope and QOL to promote their wellbeing. Many participants in the experimental
group indicated that they were grateful for the project and that the HIP enhanced their
knowledge of hope and the resources available to improve and maintain their health and
well-being.
Essential VIII: Advanced Nursing Practice
One of the goals of an advanced nurse is to contribute positively to optimal
patient care through evidence-based therapeutic interventions. Advanced nurses with a
DNP degree are paving the way and influencing patient care each and every day (Chism,

80
2019). The project manager was able to demonstrate advanced thinking in identifying and
incorporating theory, best practice, and in implementing an intervention with the
identified population based on the literature findings. Health professionals should
continue to evaluate the outcomes of this intervention in order to add to the knowledge,
bridge the gap, and promote hope and QOL in the senior population.
Conclusion
This project was conducted during the COVID-19 pandemic in order to bridge the
gap in the knowledge of the effects of the Hope Intervention Program on hope and QOL.
COVID-19 affected many, especially those that were elderly and lived alone. They were
isolated and experienced greater levels of feelings of loneliness, fear, depression, despair,
hopelessness, and abandonment (Kasar et al., 2020).
The project addressed the essential needs of the growing elderly population in
order to improve the levels of hope and QOL by utilizing the HIP during these
challenging times. Even though the data demonstrated no statistical insignificance in
improving hope and QOL after the intervention, many seniors still wanted to get out of
the house and be supported by others. This theme came out repeatedly during the
sessions, positively affecting others who were unsure of the in-person sessions. The
participants were provided with resources that are available in the community to assist
seniors. This study gave an opportunity for the elderly in the community to enjoy life
again through coming together, sharing, discussion, learning, connecting with others, and
building new relationships.

