


1
Chapter 1: Introduction to the Study
Introduction
In this study, I examined the moderating effect of social support (perceived
supervisor support and perceived organizational support) on the relationship between
occupational distress and somatic symptoms among Catholic clergy in the United States
using the stress-buffering model of social support as the theoretical framework. Members
of helping professions, such as clergy, are particularly vulnerable to the adverse effects of
occupational stress on actual health outcomes (Tice et al., 2021). The relationship
between occupational stress, social support, and somatic symptoms is essential in making
predictions regarding health outcomes, including chronic disease and poor mental health
(Eagle et al., 2019; LaRocco et al., 1980; Ozbay et al., 2007). Actual health outcomes
such as chronic disease and poor mental health interfere with the daily functioning of
clergy and the wide variety of skilled roles they perform (Doolittle, 2007; Tice et al.,
2021). Clergy exhibit significantly higher rates of stress, mortality, and chronic disease
diagnosis (diabetes, arthritis, high blood pressure, angina, and asthma) in comparison to
their nonclergy counterparts (Proeschold-Bell & LeGrand, 2012; Tice et al., 2021). These
high rates of stress, as well as their severity, often produce distress, which is stress that
has negative effects on the body and mind (Bienertova-Vasku et al., 2020; Chu et al.,
2024; Lu et al., 2021; Selye, 1974). Although research on occupational stress and social
support has been conducted, the moderating effect of social support on the relationship
between occupational distress and somatic symptoms among Catholic clergy in the
United States has been understudied. Understanding the relationships between social

2
support, occupational distress, and somatic symptoms is critical as their impact affects
both the well-being of clergy and their capacity to meet the social, cultural, spiritual, and
religious needs of parishioners.
Through this study, I aimed to narrow the gap in the literature by examining
whether social support (perceived supervisor support and perceived organizational
support) moderates the relationship between occupational distress and somatic symptoms
in Catholic clergy living in the United States. The roles of Catholic clergy differ
significantly from those of other professions. For instance, priests often struggle to find a
balance between their professional and personal lives compared to individuals in other
occupations (Ruiz-Prada et al., 2021). Unlike other professions, Catholic clergy do not
have a clear delineation between work life and nonwork life (Zickar et al., 2008).
Therefore, clergy are constantly exposed to occupational stress, even when they are not
directly engaged in their occupational roles.
This study enhances the understanding of the relationship between occupational
distress, social support, and somatic symptoms among clergy by using the stress-
buffering model as the theoretical framework. The results suggest that while supervisor
support can decrease the somatic symptoms associated with occupational distress,
organizational support can increase these symptoms. The insights gained can assist in
developing targeted interventions to ensure the well-being of clergy (Ruiz-Prada et al.,
2021). This study contributes to the body of knowledge on clergy health by highlighting
the significant moderating roles of supervisor and organizational support, and it suggests
areas for future research to provide a more comprehensive understanding of clergy well-

3
being. This supports the views of Miles and Proeschold-Bell (2013), emphasizing the
importance of tailored support systems in mitigating stress-related health issues among
clergy.
In Chapter 1, I discuss the background of the study and present the problem
statement along with the purpose of the study. The research questions and hypotheses
together with a theoretical model and nature of the study are reviewed in this section.
This chapter also includes a discussion of the operational definitions, assumptions, and
scope and delimitations. The chapter will then highlight the limitations and significance
of the study.
Background
Frequent relocation, lack of privacy, heavy demands on their time and physical
energy, and criticism from parishioners and other clergy are examples of work-related
stressors that can cause occupational stress for priests (Miles & Proeschold-Bell, 2013).
Wells (2013a) examined whether time spent in the ministry and the age of the clergy
predicted actual health outcomes. The researchers concluded that age and time in
ministry were significant predictors of the health status of clergy populations. The
researchers also found that the emotional and physical health status of clergy increased
when social support increased. Health outcomes were indicated by the rates of chronic
diseases related to clergy occupation, with positive health outcomes indicating a lower
rate of chronic disease. In contrast, adverse health outcomes showed higher rates of
chronic disease. The negative health outcomes associated with stress affected the clerical
capacity to perform parish duties (Wells, 2013a, 2013b).

4
Lin et al. (1979) described social support as the accessible support available from
individuals, groups, and communities due to their social ties. Others have defined it as the
individual's social network's support (emotional, instrumental, and informational) that is
available to help the individual cope with stress (Cohen, 2004). Studies that explored the
relationship between social support and its stress-related protective factors among
different types of populations concluded that one of the more important protective factors
against stress is social support (Cohen et al., 1986; Cohen & Wills, 1985; Shaw et al.,
2021). A study by Shaw et al. (2021) found that increased levels of social support were
associated with lower rates of stress and improved health outcomes, specifically
decreased depression levels, among clergy. This suggests that social support may play a
crucial role in promoting the mental health and well-being of this population. According
to several studies, social support has been found to be perceived by clergy as a means of
coping with the daily stressors associated with their profession (Bricker & Fleischer,
1993; Edwards et al., 2022; Pietkiewicz & Bachryj, 2016). However, Ruiz-Prada et al.
(2021) also revealed that a considerable proportion of Italian Catholic priests (23%)
reported feeling discouraged due to a lack of support and continued to report a lack of
social support from parishioners and collaborators, as well as a lack of networking with
other colleagues, as factors that worsened the occupational stress they were already
experiencing in their jobs.
Trevino and McConnell (2014) explored the relationship between religious
coping styles and health outcomes in patients with cardiovascular disease. The authors
defined positive religious coping as the act of seeking the presence of God when faced

5
with stress, whereas negative religious coping was the act of rejecting the presence of
God when faced with stress (Trevino & McConnell, 2014). It was observed that positive
religious coping, including strategies such as seeking spiritual support from God, clergy,
and church members, decreased the levels of stress and improved quality of life.
Kane (2017) conducted research to determine how active priests (N = 18) felt
about the physical and cognitive changes that come with age, the stress in their life, and
the need of self-care. The study showed that 68% of clergy lacked confidence in their
bishop and his abilities as a leader of diocesan pastoral activity. Similarly, 59% of
participants indicated that they received little or no support from their bishop in response
to excessive or unreasonable demands from parishioners that greatly exceeded their
abilities and availability (Kane, 2017). Kane's findings were backed by a more recent
study by Ruiz-Prada et al. (2021), who conducted an exploratory review of the literature
on the occupational stress of Catholic priests. The purpose of their quantitative cross-
sectional study was to measure the clergy occupational distress, social support, mental
health, and spiritual wholeness of clergy in Florida. Compared to national averages,
clergy in this study displayed higher levels of occupational stress and depression (Ruiz-
Prada et al., 2021). According to the authors, these results should raise broad concerns
regarding the mental health of clergy and the support that is available to them (Ruiz-
Prada et al., 2021). The study also demonstrated that comprehensive assessments of
validated instruments such as the Clergy Occupational Distress Index (CODI) and the
Patient Health Questionnaire (PHQ-9) can provide insight into the health of clergy.

6
Proeshold-Bell and LeGrand (2012) conducted a comparative study on clergy and
nonclerical populations in which they explored the association between health
perceptions and actual health outcomes (e.g., chronic disease rates). Proeshold-Bell and
LeGrand (2012) categorized the clergy population as parish leaders who had at least 5
years of service in the ministry. The nonclergy population comprised any other
population not serving in a parish (Proeshold-Bell & LeGrand, 2012). The clergy
populations had lower actual health outcomes demonstrated by higher rates of chronic
diseases compared to the nonclergy populations. Furthermore, clergy populations had
optimistic perspectives on health perceptions that resulted in unrealistic health outcomes.
The authors recommended further examination of the relationship between health
perceptions among clergy populations and actual health outcomes (Proeschold-Bell &
LeGrand, 2012).
Ruiz-Prada et al. (2021) conducted a review of the literature on the relationship
between the experience of stress and burnout syndrome among Catholic priests. The
study found that Catholic priests encounter a variety of risk factors associated with work-
related stress, including distrust from society, lack of sufficient support, living alone,
complacent and avoidant coping styles, excess demands, and unclear boundary between
priestly roles and life roles. These risk factors are responsible for the increased stress and
burnout that Catholic priests undergo in their priestly role. The studies in the review also
identified significant protection factors such as leading an active spiritual life, social
support (e.g., from superiors, colleagues, collaborators, and parishioners), strengthening
personal identity, finding enough resting time, eating a balanced diet, frequent physical

7
exercise, an approach-based coping style, and promoting optimism. The social and health
outcomes of stress and burnout among Catholic priests include alcoholism, smoking,
depression, anxiety, cardiovascular disease, diabetes, and obesity. The researchers found
that strengthening protective factors as well as minimizing the influence of risk factors
can help to improve the health outcomes of the clergy.
The consequences of stress on clergy are extensive and include harmful physical
and mental health implications (Sielaff et al., 2021). Compared to the general population,
clergy have higher rates of stress, mortality, and chronic illness diagnosis (e.g., diabetes,
arthritis, high blood pressure, angina, and asthma; Proeschold-Bell & LeGrand, 2012;
Tice et al., 2021). Despite studies on both professional stress and social support, the
relationship between occupational stress and somatic complaints among Catholic clergy
in the United States has not received sufficient attention. Even less is known about the
moderating effect of social support on the link between professional stress and somatic
symptoms in Catholic clergy. In the current study, I used the stress-buffering model of
social support to understand the moderating effect of social support on the relationship
between occupational distress and somatic symptoms among a sample of clergy (Cohen
& Wills, 1985). This study was needed to investigate the role that occupational distress,
social support, and somatic symptoms have in predicting actual health outcomes in
clerical populations due to the influence their health may have on the quality of service
they provide to their parishioners.

8
Problem Statement
According to Clarke et al. (2022), the occupational demands of their pastoral
work expose priests to conditions that result in increased occupational stress, burnout,
emotional exhaustion, feelings of isolation, and personal challenges. Additionally, Webb
and Chase (2019) found that elevated levels of occupational distress were significantly
associated with an increased risk of negative health outcomes such as high blood
pressure, diabetes, chronic stress disorder, depression, anxiety, and prolonged sitting
time. They suggested that occupational distress might negatively affect the health of full-
time Christian clergy, particularly those who are younger, and advocated for further
research on the temporal relationships among occupational distress, health, and health
behaviors among full-time clergy (Webb & Chase, 2019). Similarly, Shaw et al. (2021)
found that clergy had a depression rate of 12.9%, which is worse than the previously self-
reported rate of 11.1%, among United Methodist clergy study participants and the
published national average for 2017 of 7.9% (National Institute of Mental Health, 2019;
Proeschold-Bell et al., 2013). They also found an inverse correlation between the number
of sources of social support and depression levels among clergy (Shaw et al., 2021).
Wells (2013a, 2013b) highlighted the significance of determining the relationship
between occupational stress, health perceptions, and coping style in predicting the actual
health outcomes among the clergy population. In this context, actual health outcomes
refer to chronic diseases that include cancer, diabetes, obesity, and cardiovascular
diseases, among others. In addition, Webb and Chase (2019) found that a significant
proportion of clergy reported having chronic diseases such as high blood pressure

9
(33.5%), high cholesterol (29.0%), arthritis (15.4%), depression (14.9%), and anxiety
(12.7%), and over half of the clergy were classified as obese. Logistic regression models
demonstrated that increasing age, body mass index (BMI), and occupational distress were
associated with an increased likelihood of reporting a diagnosis of high blood pressure,
high cholesterol, type 2 diabetes, and arthritis (Webb & Chase, 2019). Harmon et al.
(2021) also noted that work-related stress and church traditions can be barriers to healthy
behaviors among clergy, including maintaining a healthy weight. The association
between occupational distress, social support, and real health outcomes among the clergy
population has been generally understudied. Only a small number of studies have been
done specifically focusing on clergy stress and their mortality rates. Even less is known
about the moderating effect of perceived social support on the relationship between
occupational distress of clergy and somatic symptoms. Somatic symptoms have been
described as predictors of poor physical health, mental health, and everyday functioning
(Bohman et al., 2018; Henningsen, 2022).
It is important to determine the extent of the relationship between occupational
distress, social support, and actual health outcomes among the clergy population because
this affects their work performance and their efficacy in serving parishioners. Research
shows that the occupational demands of the pastoral work of priests expose them to
conditions that result in the development of occupational stress (Clarke et al., 2022;
Proeschold‐Bell et al., 2015). Furthermore, role-related stress and adversity pose
significant challenges to clergy members' resilience and well-being. Researchers also
found that clergy members face complexity and ambiguity in their roles, which can lead

10
to difficulties in coping with stressors (Clarke et al., 2022). This can be attributed to the
different roles that clergy perform in their occupation. Currently, as part of their pastoral
work, priests take on many roles such as counselor, caregiver, minister, leader, role
model, speaker, church representative, administrator, supervisor, therapist, social worker,
spiritual director, educator, and negotiator (Clarke et al., 2022; Kay, 2000; Kuhne &
Donaldson, 1995; Miles & Proeschold-Bell, 2013; Pickard & Guo, 2008).
Lin et al. (1979) described social support as the accessible support available from
individuals, groups, and communities due to social ties. Others have defined it as the
individual's social network's support (emotional, instrumental, and informational) that is
available to help the individual cope with stress (Cohen, 2004). Several studies have
explored the significance of social support in mitigating the negative impact of
occupational stress among clergy. Shaw et al. (2021) found that higher levels of social
support were associated with lower levels of depression among clergy. Similarly, Webb
and Chase (2019) found that perceived social support was negatively associated with
occupational distress among Christian clergy. The study by Harmon et al. (2021)
highlighted the importance of social support in promoting healthy behaviors among
clergy and their spouses. In addition, Proeschold-Bell et al. (Eagle et al., 2019; Miles &
Proeschold-Bell, 2013) identified social support as a potential protective factor against
burnout among clergy. These findings suggest that social support may play a significant
role in reducing the negative impact of occupational stress on the mental health and well-
being of clergy. There remains a gap in the literature concerning the extent to which
social support moderates the relationship between job-related stress and somatic health

11
symptoms among clergy. Further research is needed to explore the potential protective
effects of social support in reducing the negative impact of occupational distress on
somatic health symptoms among this population. This study was designed to explore the
moderating effect of social support in the relationship between stress and somatic
symptoms among the clergy population in the United States.
Purpose of the Study
The purpose of this quantitative nonexperimental correlational study was to
examine the extent to which perceived supervisor support and perceived organizational
support moderate the relationship between occupational distress (IV) and somatic
symptoms (DV) among clergy.
Research Questions and Hypotheses
RQ1: To what extent does occupational distress, as measured by the Clergy
Occupational Distress Index, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H01: Occupational distress is not a significant predictor of somatic health
symptoms (gastrointestinal problems, headaches, sleep disturbance, and respiratory
infections).
H1: Occupational distress is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ2: To what extent does supervisor support, as measured by the Survey of
Perceived Supervisor Support, relate to somatic health symptoms (gastrointestinal

12
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H02: Supervisor support is not a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
H1: Supervisor support is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ3: To what extent does organizational support, as measured by the Survey of
Perceived Supervisor Support, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H03: Organizational support is not a significant predictor of somatic health
symptoms (gastrointestinal problems, headaches, sleep disturbance, and respiratory
infections).
H3: Organizational support is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ4: To what extent does supervisor support moderate the relationship between
occupational distress and somatic health symptoms (gastrointestinal problems, headaches,
sleep disturbance, and respiratory infections) among Catholic clergy working in the
United States?
H04: Supervisor support does not moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).

13
H4: Supervisor support does moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
RQ5: To what extent does organizational support moderate the relationship
between occupational distress and somatic health symptoms (gastrointestinal problems,
headaches, sleep disturbance, and respiratory infections) among Catholic clergy working
in the United States?
H05: Organizational support does not moderate the relationship between
occupational distress and somatic health symptoms (gastrointestinal problems, headaches,
sleep disturbance, and respiratory infections).
H5: Organizational support does moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
Theoretical Framework for the Study
Cohen and Wills (1985) conceptualized the stress-buffering model of social
support (SBMSS). The model proposes that social support mitigates the negative impacts
of stress and enhances the outcomes of stressful experiences (Cohen et al., 1986). It also
posits that social support can protect against or mitigate the negative consequences of life
stress that are likely to have an adverse impact on mental health. According to this model,
the mitigating effects are most pronounced when individuals are under extreme stress and
feel that support is available and offered on demand. This model, also referred to as the

14
stress-buffering hypothesis, asserts that social support modulates the link between
perceived stress, health, and disease.
The approach permits researchers to examine whether the perceived availability
of social support protects individuals from stress and improves outcomes that may impact
their well-being (Cohen & Wills, 1985). The premise of the SBMSS model is that some
resources can mitigate the impact of negative life events on a person's health state. When
unpleasant occurrences occur regularly, they can add up and cause health issues.
However, life stress may have less of an effect on those with greater psychosocial
resources, which may function as a buffer or insulator between the stressors and the
health effects (Ditzen & Heinrichs, 2014). Thus, those with greater resources suffer less
stress. Stress can also be caused by job stresses in high-demand, low-control
organizations. Most research conducted on nonclergy groups has associated elevated
stress levels with sadness, anxiety, and physical ailments (Creswell et al., 2014).
However, buffering resources can substantially reduce the negative health effects of
stress (Creswell et al., 2014).
Nature of the Study
The study was quantitative in nature as it was appropriate to examine the
relationships among variables. A nonexperimental correlational design was utilized to
determine the extent to which perceived supervisor and organizational support moderate
the relationship between occupational distress (IV) and somatic symptoms (DV) among
the clergy. A cross-sectional strategy is typically used in surveys when data are collected
at one point in time as opposed to data collected over time (Vicente-Galindo et al., 2017).

15
The choice of survey was based on the rationale that it is most practical and effective in
collecting data from a large population (Vicente-Galindo et al., 2017).
The population of the study was Catholic priests who had practiced their
profession in the United States for at least 2 years, were at least 27 years old, and were
currently living in the United States. Convenience sampling, which is a nonprobability
sampling strategy, was used to recruit a sample of clergy who met the inclusion criteria
for participation. The data were uploaded and analyzed using the Statistical Package for
Social Sciences (SPSS) version 27.0 software. Standard multiple regression analysis (i.e.,
enter method) was used to determine the extent to which perceived supervisor support
and perceived organizational support moderate the relationship between occupational
distress and somatic symptoms among Catholic clergy.
Definitions
Stress: The body's nonspecific response to any demand placed upon it. The stress
response is a complex biological and psychological reaction aimed at restoring balance or
homeostasis (Selye, 1956).
Occupational stress: Stress experienced in the workplace, leading to adverse
emotional and physiological effects such as anxiety, depression, and burnout. It impairs
an individual's well-being and productivity (Le Fevre et al., 2003).
Clergy occupational stress: Stress that clergy experience due to unique stressors
related to their profession, including excessive demands from congregation members,
personal criticism, feelings of loneliness or isolation, and challenges faced within their
congregation (Frenk et al., 2013).

16
Perceived social support: The perceived availability, adequacy, and quantity of
different types of support (emotional, practical, informational, and financial; Nazari et al.,
2020).
Perceived supervisor support: The employee’s perception that the supervisor
values their contribution and cares about their well-being (Eisenberger et al., 2002).
Perceived organizational support: The employee’s perception that the
organization values their contribution and cares about their well-being (Eisenberger et al.,
2002).
Somatic symptoms: Involuntary physical symptoms that occur in response to
psychological and emotional distress, typically without a biological cause (Kurlansik &
Maffei, 2016). Different terms have been proposed, such as somatization, unexplained
somatic complaints, somatoform disorders, and somatic symptom disorder (Alalawi et al.,
2022; American Psychiatric Association, 2013; Kramer et al., 1979). Somatic symptoms
have also been defined as a type of physical strain (Schat et al., 2005).
Catholic priest: A member of the clergy ordained to the sacerdotal or pastoral
office by the Catholic church. Historical views of priests include spiritual teachers,
professors, writers, and counselors (Zickar et al., 2008). Currently, as part of their
pastoral work, priests take on many roles such as counselor, caregiver, minister, leader,
role model, speaker, church representative, administrator, supervisor, therapist, social
worker, spiritual director, educator, and negotiator (Kay, 2000; Kuhne & Donaldson,
1995; Miles & Proeschold-Bell, 2013; Pickard & Guo, 2008).

17
Assumptions
There were several relevant assumptions in this study. The first assumption was
that participants would respond to the survey questions honestly. The data collection
process was designed to maintain anonymity and confidentiality to promote honest
responses when completing the survey. The final assumption was that there would be no
researcher bias that could potentially contaminate the data.
Scope and Delimitations
The scope of this study was on occupational distress, perceived supervisor
support, perceived organizational support, and somatic symptoms using the stress-
buffering model of social support. The main objective of this study was to assess if
perceived supervisor support and perceived organizational support have a moderating
effect on the relationship between occupational distress and somatic symptoms among
Catholic clergy. This population is significantly different from other occupational groups
in that Roman Catholic priests generally regard their work roles as a vocation rather than
a job (Zickar et al., 2008). The sample was comprised of and limited to priests over the
age of 27 who had at least 2 years of experience as a priest and had lived in the United
States for the last 3 years.
Limitations
Because the study used convenience sampling, the representativeness of the
sample and, therefore, the generalizability of the results may have been limited,
guaranteed only when participants are randomly selected. Another limitation of this study
was social desirability. Social desirability is the conscious or unconscious need to

18
respond in a socially or culturally appropriate manner (Larson, 2019). In some instances,
it may be used to make oneself or, in this instance, one's occupation or field, appear more
favorable. Priesthood is generally viewed negatively by a portion of the population. This
should be acknowledged, as the priest may feel obligated to respond in a socially or
culturally appropriate manner. To reduce the likelihood of social desirability
contaminating the data, the study reinforced the idea that all information submitted by the
participant was anonymous; no identifying information was collected, nor was their
location identified.
Significance
Clergy exhibit significantly higher rates of stress, mortality, and chronic disease
diagnosis (diabetes, arthritis, high blood pressure, angina, and asthma) in comparison to
their nonclergy counterparts (Proeschold-Bell & LeGrand, 2012; Tice et al., 2021).
Although research on occupational stress and social support had been conducted, the
moderating effect of social support on the relationship between occupational distress and
somatic symptoms among Catholic clergy in the United States was understudied. In this
study, I examined the extent to which social support moderates the relationship between
occupational distress and somatic symptoms among Catholic clergy. The study may lead
to positive social change by adding new data to the limited amount of literature on the
clergy population. Furthermore, this study can help employers, organizations, and health
agencies create better social support strategies focused on the needs of the clergy
population and other high-stress occupations. This would be beneficial to the clergy as

19
well as the parishioners they serve because occupational distress has a significant
influence on daily functioning of the clergy.
Summary
Occupational stress develops from the inability to cope with the demands of the
workplace due to the lack of availability and may negatively impact a person's physical
health and mental health and increase their risk of occupational distress. The occupational
roles of Catholic clergy are significantly different from those of other occupational
populations. For example, a delineation between work-life and nonwork life exists in
other occupations, which is not the case for priests. The purpose of this study was to
examine the moderating effect of social support on the relationship between occupational
distress and somatic symptoms among Catholic clergy, a population that is significantly
different from other occupational groups covered in most studies.
Chapter 2 provides a description of the literature search strategy followed by a
discussion of the stress-buffering model of social support, which served as the theoretical
framework. This chapter also provides a thorough review of the current literature on the
roles of Catholic clergy in the United States, occupational stress among clergy, social
support, and somatic symptoms and health among clergy.

20
Chapter 2: Literature Review
Introduction
Catholic priests are part of a professional group in which interaction and social
function are particularly important to their church, parish (ecclesiastical territory), and the
people who are part of the parish (i.e., parishioners; Vicente-Galindo et al., 2017).
Research has shown that the occupational demands of their pastoral work expose priests
to conditions that result in the development of occupational stress (Madukwe et al., 2019;
Miles & Proeschold-Bell, 2013). As part of their pastoral work, priests take on many
roles such as a counselor, caregiver, minister, leader, role model, speaker, church
representative, administrator, supervisor, therapist, social worker, spiritual director,
educator, negotiator, and local community leader (Kay, 2000; Kuhne & Donaldson, 1995;
Miles & Proeschold-Bell, 2013; Pickard & Guo, 2008; Zembylas et al., 2019).
Research shows that the numerous responsibilities clergy must accomplish within
faith-based organizations may put them under a great deal of psychosocial stress (Kay,
2000; Kuhne & Donaldson, 1995; Miles & Proeschold-Bell, 2013; Pickard & Guo, 2008;
Ruiz-Prada et al., 2021; Zembylas et al., 2019). Frequent relocation, lack of privacy,
heavy demands on their time and physical energy, and criticism from parishioners and
other clergy are additional work-related stressors that can cause occupational stress
among priests (Miles & Proeschold-Bell, 2013; Ruiz-Prada et al., 2021). Additionally,
members of helping professions, such as clergy, are particularly vulnerable to the adverse
effects of occupational stress on actual health outcomes (Tice et al., 2021). The
relationship between occupational stress, social support, and somatic symptoms is

21
essential in making predictions regarding health outcomes, including chronic disease and
poor mental health (Eagle et al., 2019; LaRocco et al., 1980; Ozbay et al., 2007).
Therefore, the purpose of this quantitative study was to address a gap in the literature by
determining the extent to which perceived social support moderates the relationship
between occupational stress (IV) and somatic symptoms (DV) among clergy working in
the United States.
According to the National Institute for Occupational Safety and Health (1999),
occupational stress is defined as the stress that an individual develops due to
misalignment between the needs of a job and the capabilities of the worker, accessible
resources, and the expectations of the hiring company or organization. Under the person–
environment fit theory, occupational stress results from a mismatch between the
employee's capabilities and the expectations of the work environment. This mismatch
may be the result of the individual's aptitudes and skills not matching those required by
their profession or their employment failing to meet their specific requirements and
expectations (de Mézerville, 2012; Luceño Moreno et al., 2004; Ruiz-Prada et al., 2021).
Additionally, research has shown that occupational stress developed from factors
in the psychosocial work environment has been linked to the development of workers'
adverse physical and emotional responses (Melchior et al., 2007; Ruiz-Prada et al., 2021).
Several studies have assessed different occupational work environments and confirmed
that a high-stress work environment is a predictor of poor health and well-being (Ibrahim
et al., 2021; Kaburi et al., 2019; Sonnentag, 2018; Yu et al., 2008). Some of the factors
that demonstrated a link with poor well-being were occupational stress, high work

22
demands, inadequate job stability, low reward, and low social support (Ibrahim et al.,
2021; Kaburi et al., 2019; Sonnentag, 2018; Yu et al., 2008).
Various studies have focused on the factors that affect the health of the clergy
population. For example, a study reported that stress negatively impacts priests' overall
health, reducing their engagement in healthy behaviors (Proeschold-Bell & LeGrand,
2012). The quantitative study examined the physical health functioning among a sample
of clergy and compared it to a nonclergy population. Results showed that clergy exhibit
higher rates of chronic diseases compared to their nonclergy counterparts (Proeschold-
Bell & LeGrand, 2012). Other researchers have also identified a clear relationship
between an individual’s stress level and health outcomes (Proeschold-Bell et al., 2011). It
was also observed that the way that clergy cope with pastoral stress can positively or
negatively impact their health (Proeschold-Bell & LeGrand, 2012). The stress-buffering
model is frequently used by researchers to assess whether the perceived availability of
social support buffers stress levels and consequently improves well-being (Cohen &
Wills, 1985).
Researchers have also pointed out that social support may decrease the prevalence
of occupational stress and reduce the impact of stressors (Viswesvaran et al., 1999).
Thus, the effects of occupational stress and related stressors may be different depending
on the availability of resources and personal characteristics of the priest (Carroll, 2006;
Dewe, 1987; Rodgerson & Piedmont, 1998). A meta-analysis conducted by Viswesvaran
et al. (1999) on the different models for the role of social support in the process of work
stress found that social support decreased the strains experienced, lessened perceived

23
stressors, and moderated the stressor–strain relationship. While research on the negative
impacts of occupational stress on health exists, there is a gap in the existing literature
needed to determine how social support affects the relationship between occupational
stress and health among priests.
Chapter 2 begins with a description of the literature search strategy followed by a
discussion of the stress-buffering model of social support, which served as the theoretical
framework. The literature review includes discussions pertaining to the roles of Catholic
clergy in the United States, occupational stress among clergy, somatic symptoms and
health issues among clergy, and social support. A summary section will be included to
provide an explanation of the gap in literature and how I attempted to fill that gap through
the present study.
Literature Search Strategy
The databases used in the search were EBSCO Host, PubMed, Google Scholar,
ProQuest, APA PsycEXTRA, APA PsycARTICLES, and APA PsycINFO. The articles
searched spanned from the 1980s to the present, with most studies focusing on
occupational stress and health issues. The key search terms and their combinations were
clergy disease, clergy health, clergy stress, life stress, social support, clergy coping,
chronic diseases, health outcomes, somatic symptoms, secondary trauma, secondary
traumatic stress, vicarious trauma, compassion fatigue, coping styles, health perceptions,
religious coping, organizational support, self-regulation, stress-buffering, physical
health, and emotional health. Other combinations used in the search were Catholic clergy
burnout, burnout clergy, burnout Catholic clergy, Catholic priests and secondary stress,

24
compassion fatigue in priests, priests and secondary trauma, chaplains and vicarious
trauma, clergy stress, clergy occupational stress, clergy somatic symptoms, clergy social
support, and priests' somatic stress and social support. For a more refined search, the key
terms used were compassion fatigue and compassion satisfaction, secondary traumatic
stress and life satisfaction, social support and secondary traumatic stress, clergy stress
and self-care, emotional intelligence and the clergy, trauma counseling, clergy mental
health, and clergy indirect trauma.
Theoretical Foundation
The stress-buffering model of social support (SBMSS) was developed by Cohen
and Wills (1985). The model asserts that social support buffers the detrimental effects of
stress and improves the outcomes of stressful events (Cohen et al., 1986; Cohen & Wills,
1985). The model holds that social support can offer protection or moderate the adverse
effects of stress experienced in life likely to affect mental health. According to this
model, the moderating effects are most significant when people are under high duress and
perceive that support will be offered on demand. Otherwise known as the stress-buffering
hypothesis, this model claims that social support influences the relationship between
perceived stress, health, and disease.
The model allows researchers to study whether the perceived availability of social
support protects persons from stress and improves the outcomes that may affect their
well-being (Cohen & Wills, 1985). The concept underlying the SBMSS model is that
some resources are beneficial in reducing the influence of adverse life events on a
person's health status. When adverse events occur repeatedly, they can accumulate and

25
bring about health problems. However, life stress may have less impact on individuals
with more psychosocial resources where the resources serve as a buffer or insulating
factors between the stressors and the health outcomes (Ditzen & Heinrichs, 2014).
Consequently, individuals with more resources experience stress to a lesser extent. One
way stress is measured is through the number of adverse events that a person has
experienced over a specific duration (Ditzen & Heinrichs, 2014). Some of the adverse
events may include severe financial difficulty, loss of a loved one, and job-related strains,
among others. Job strains in workplaces with high work demand and low control can also
be sources of stress. Elevated stress levels have been linked with depression, anxiety, and
physical problems, according to most studies conducted on nonclergy populations
(Creswell et al., 2014). However, the buffering resources can significantly minimize the
adverse health effects of stress (Creswell et al., 2014).
Various types of stress-buffering agents exist, one of them being social support.
The buffering effect, or moderator, is often referred to as both moderator and mediational
and suppressor effects (Viswesvaran et al., 1999). Viswesvaran et al. (1999) conducted a
meta-analysis on the different roles of social support in the process of work stress and
identified that social support had a moderating effect on strains experienced, lessened
perceived stressors, and moderated the stressor–strain relationship. For example, social
support moderates the effects of occupational stress of workers (Viswesvaran et al.,
1999). Perceived organizational support and perceived supervisor support have also been
shown to moderate the effects of stress. Jain et al. (2013) investigated the influence of
perceived organizational support as a moderator in the relationship between organization

26
stressors and organizational citizenship behaviors among operator-level employees
working within the business process outsourcing sector in India. Perceived organizational
support had a significant positive relationship with occupational stress, which improved
the psychological and emotional well-being of employees (Jain et al., 2013).
Evidence of the stress-buffering effect of social support was found in a study that
researched the effects of occupational stress on the mental health of a sample of 325 male
power plant employees (Bromet et al., 1988). A significant moderating effect was
observed from social support between occupational stress and the psychological and
emotional well-being of employees. The study found that workers with higher workplace
stressors had a higher probability of experiencing an episode of affective disorder if they
received lower levels of coworker support; if higher levels of coworker support were
received, workers with higher workplace stressors had a lower probability of
experiencing an episode of affective disorder (Bromet et al., 1988).
Among clergy, Proeschold-Bell et al. (2015) found a significant relationship
between work-related stress and mental health. Results indicated that social support
buffered the negative impact of work-related stress on the mental health among clergy.
Wells (2013) conducted a study that explored the relationship between stress and the
health of clergy and discovered that congregational and denominational support were
moderators that decreased the adverse effects of stress on the health of clergy. Zickar et
al. (2008) investigated the relationship between role stressors and job attitudinal variables
and the potential moderating influence of social support in a sample of 190 Roman
Catholic priests and found that role stressors resulted in negative job attitudes such as

27
turnover intention and low job satisfaction (Zickar et al., 2008). The study applied the
stress-buffering hypothesis focusing on several sources of social support and found that if
priests had sources of social support, there was a higher probability that it buffered the
adverse effects of occupational stress on job satisfaction and their intentions to quit.
Thus, the stress-buffering model can be applied to Catholic clergy populations to evaluate
the moderating effect of social support on the relationship between occupational stress
and health.
Literature Review Related to Key Variables and/or Concepts
Role of Catholic Clergy
The Roman Catholic church has a unique organizational structure (Nkonge
Kagema, 2012). This church is a global organization with a hierarchical structure that
moves from the Vatican to the local dioceses (Kane & Jacobs, 2017). The leader of each
local church is the bishop, who is in a leadership role supervising the priests. The bishop
also manages the property owned by the local church. The Pope appoints the bishop and
determines the local church to which they are posted. The bishop is considered the final
decision-maker and authority for the local church with the assistance of his curia (i.e.,
priests serving as officials who assist the diocesan bishop). The other function of the local
bishop is overseeing the ecclesial staff. The bishop works closely with the priests who are
assigned day-to-day duties in different ministries or parishes. Priests are ordained and
assigned from one church to another by the bishops (Kane, 2008). The role of the priest is
to represent the bishop at the local parish, undertaking responsibilities such as offering
pastor services and spiritual care (Kane, 2008). The roles of priests have changed over

28
time. Priests have been viewed historically as spiritual teachers, professors, writers, and
counselors (Zickar et al., 2008). As part of their pastoral work, priests take on many roles
such as counselor, caregiver, minister, leader, role model, speaker, church representative,
administrator, supervisor, therapist, social worker, spiritual director, educator, and
negotiator (Kay, 2000; Kuhne & Donaldson, 1995; Miles & Proeschold-Bell, 2013;
Pickard & Guo, 2008).
The structure of the Catholic church follows the servant-leadership model (Joo et
al., 2018; Tran & Spears, 2020). This structure was proposed and designed in the early
centuries of the western and eastern patristic literature (Kgatle, 2015; Niewold, 2007).
This model is inscribed in modern theological and spiritual writings (Kane, 2014).
Furthermore, this model is also referenced in the New Testament through the teachings of
Jesus Christ. While the servant-leadership model implies that leaders should be humble
and willing to serve all people, priests and their congregations are encouraged by the
Catholic tradition to consider the bishop as the spiritual father in their dioceses (Kane,
2014). The patristic as well as theological teachings have long stressed the need for
respectful and loving leadership that is embedded in the New Testament teachings
(Patterson, 2010). Patience, equality, trust, kindness, respect, and love in the Biblical
teachings underpin the qualities of respectful leadership (Anderson, 2021). Van
Quaquebeke and Eckloff (2010) advanced the respectful leadership qualities that have
striking similarities with the spiritual leadership qualities highlighted in scriptures. These
authors suggested that respectful leadership comprised behaviors such as being error-

29
friendly, acknowledging equality, considering needs, conferring responsibility, valuing,
and trusting.
Respectful leadership holds that subordinates who feel respected by their
superiors are more likely to work hard toward the goals of the organization compared to
those who feel disrespected (Kane & Jacobs, 2017). Further, the clergy are likely to
perceive their activities positively as well as record fewer physical, psychological, and
emotional complaints (Kane & Jacobs, 2017). Bishops, in their part, can demonstrate
respectful leadership consistent with research and New Testament teachings by
demonstrating behaviors that foster respect. Bishops can also show they value individuals
within their laity. They should share power and responsibility as well as encourage
approachability from the congregation and other personnel within the congregation. The
role stressors experienced by Catholic church leaders such as bishops can have a negative
impact on the clergy's health, ministerial careers, and the functioning of their
congregation as a result of occupational stress.
Occupational Stress Among Clergy
Prasad and Vaidya (2020) defined occupational stress as pressure on employees
caused by factors associated with the employment. Other researchers have found that the
occupational demands of the pastoral work of priests expose them to conditions that
result in the development of occupational stress (Proeschold‐Bell et al., 2015). These
researchers explained that frequent relocation, lack of privacy, heavy demands on their
time and physical energy, and criticism from parishioners and other clergy are additional
work-related stressors that can cause occupational stress among priests. Proeschold-Bell

30
et al. (2015) used a sample of church-appointed clergy (N = 1,476) to examine the
variables (e.g., clergy-specific variables, variables shown to relate to affect across
populations, demographics, and social desirability) that may reduce negative mental
health and increase positive mental health. Social support, social isolation, and financial
stress were directly related to the level of mental health of clergy and had a larger effect
size than other variables. Financial stress, social isolation, and social support together
explained between 34% and 8% of the variance in both negative and positive affect
outcomes. Thoughts of leaving the ministry and congregation demands were significantly
related to both negative and positive affect.
Clarke et al. (2022) conducted a qualitative descriptive study to explore the types
of adversity that Christian clergy members face and their resilience. The researchers
utilized a national survey, one-on-one interviews, and interpretation panels to collect data
from 12 current or former Christian clergy members. Various types of adversity that
clergy encounter were identified through the study, including unrealistic expectations
from congregations, high workload and emotional labor, financial pressure, and
denominational expectations (Clarke et al., 2022). The findings showed that role-related
stress and adversity pose significant challenges to clergy members' resilience and well-
being. The researchers found that clergy members face complexity and ambiguity in their
roles, which can lead to difficulties in coping with stressors (Clarke et al., 2022). One of
the themes identified was isolation, which may contribute to social support being an
important factor for clergy members' resilience (Clarke et al., 2022). The study affirmed
that role complexity is a form of adversity that clergy members face, which can impact

31
their resilience and well-being (Clarke et al., 2022). In conclusion, this study provided
insights into the challenges that clergy members encounter and highlights the importance
of social support to enhance their resilience and well-being.
The working relationship between Catholic bishops and their priests has been
noted by Kane and Jacobs (2017) as a potential source of occupational stress.
Historically, the relationship between bishops and their priests have been strained
because of allegations of sexual abuse priests endured in 2002 (Kane & Jacobs, 2017).
According to survey research conducted by the Center for Applied Research in the
Apostolate, the relationship between priests and their bishops had deteriorated following
the 2002 media revelations accusing priests of sexually abusing children that was covered
up by the church (Gautier et al., 2012). After the child-abuse scandal, the survey showed
that 68% of priests reported that they had little confidence in their assigned bishops, who
they believed failed to protect them from allegations that they were sexually abusing
children. The survey also demonstrated that 64% of priests believed that the church was
not being handled properly. Of the participants, 35% of the priests reported having a
strained relationship with their bishops, while 59% indicated that they received minimal
support from their bishops. They have also had problems with the management of the
church and received little support, further exacerbating their relationship with bishops
(Gautier et al., 2012).
Another type of occupational stressor that can lead to occupational stress for
Catholic clergy is perceived social isolation (Ford, 2017). Perceived isolation and
loneliness are prevalent among priests, even if their vocational roles allow them to be in

32
constant contact with others (Ford, 2017). Using secondary data from a clergy health
intervention collected by Duke University, Ford (2017) examined the relative effects of
various measures of social relationships on physical and mental health of a clergy
population (N = 616). The results were analyzed using a hierarchal multiple regression
using three phases to control for measures of perceived social relationships (i.e.,
relationship satisfaction, social isolation, social engagement, and social support), clergy
working environment (i.e., clergy works alone of with colleagues), and demographics.
After controlling for demographics, positive correlations were found between social
engagement and positive mental health/flourishing, life satisfaction, and ministry
satisfaction. A positive correlation between social isolation and depression was also
observed (Ford, 2017).
An 18-month evaluative study was conducted by Scott and Lovell (2015) with
rural pastors (N=51) to help them deal with occupational barriers (i.e., loneliness,
seclusion, stress, work-life imbalance, and an absence of self-care activities). Findings
showed that rural pastors suffered a significant degree of loneliness and isolation and that
pastors suffering from isolation reported difficulty in maintaining a healthy work-life
balance and experienced burnout. Consistent with other literature, people are more likely
to experience mental and physical health risks if they feel a higher degree of loneliness
(Cacioppo et al., 2006).
Milstein et al. (2019) examined the relationship between spiritual well-being,
occupational distress, and depressive symptoms in a longitudinal study that targeted a
sample of 895 United Methodist clergy. Researchers measured the potential relationships

33
among spiritual well-being, occupational distress, and depressive symptoms while
controlling for social support. The sample was composed of clergy who took part in both
the 2010 and 2011 Spirited Life surveys, labeled in the study as Time 1 and Time 2
(Milstein et al., 2019). These three variables were significantly correlated, where each
variable affected or depended on another during Time 1. The prospective effects between
Time 1 and Time 2, which was a year later, were then assessed using residualized change
linear regression models. Higher levels of spiritual well-being provided protection against
increases in depressive symptoms even when research iLimberlers controlled for
perceived emotional support. A longitudinal as well as directional pattern was observed
where lower spiritual well-being predicted higher levels of depressive symptoms which
in turn predicted higher levels of occupational distress (Milstein et al., 2019).
Clergy can experience instances of spiritual dryness that can cause occupational
distress associated with depression, poor psychological health, decreased work
engagement, and life dissatisfaction (Büssing et al., 2013). These authors defined
spiritual dryness as a situation in which clergy feel they lack a spiritual feeling or a
disconnection from God. Büssing et al. (2013) developed and tested the Spiritual Dryness
Scale using data from a sample of Catholic priests (N = 425). The findings showed that
40% of priests reported having experienced occasional spiritual dryness while 13%
experienced it regularly. Occupational factors such as low control over their duties,
devaluation by superiors, and work burden can impair the positive spiritual feelings that
priests are supposed to exhibit. Consequently, they can feel a sense of being abandoned
by God or a spiritual crisis leading to occupational stress (Büssing et al., 2013).

34
Social Support Among Clergy
Lin et al. (1979) described social support as the accessible support available from
individuals, groups, and communities due to their social ties. Others have defined it as the
individual's social network's support (i.e., emotional, instrumental, and informational)
that is available to help the individual cope with stress (Cohen, 2004). The stress-
buffering model is frequently used by researchers to explain the relationship between
social support and health outcomes (Proeschold‐Bell et al., 2015). This model allows
researchers to assess whether the perceived availability of social support buffers the
levels of stress and consequently improve its effects on well-being (Cohen & Wills,
1985).
Researchers have shown that having social support protects against the
detrimental impacts of stress on both mental and physical health (Cohen & Wills, 1985;
Szkody et al., 2021). Willis and Cohen (1985) found that a buffering effect (i.e., buffering
model) was present when the interpersonal resources (i.e., source of support) was
responsive to the specific needs elicited by the stressful situation. It was determined that
social support could only assist if it corresponds to the coping strategies suitable in a
stressful situation (Cohen & Wills, 1985). For example, if a supervisor is not being
supportive, it is unlikely that a buffering effect will be found between the social support
available and the effects of occupational stress or stressors.
Further research showed that there was a stronger correlation between perceived
social support and health outcomes than with actual support received (Cohen & Wills,
1985). This implies that when participants perceived that support was available, they

35
experienced improved mental and physical health outcomes even when actual support
was not offered. Because perceived social support is a difficult to define multifaceted,
complex concept, a specific agreed-upon definition has not been established (Nazari et
al., 2020); however, it is essential to understand the concept of perceived social support
and its impact on health. Researchers commonly describe it as the perceived availability,
adequacy, and quantity of different types of support (e.g., emotional, practical,
informational, and financial; Nazari et al., 2020). For example, studies have shown that
regardless of whether people receive the same levels of support, they may have different
perceptions of the support (e.g., amount, type, quality) they are receiving (Haber et al.,
2007).
In a qualitative descriptive study, Bricker and Fleischer (1993) explored the
experiences of perceived social support among a sample of Roman Catholic priests.
These researchers designed the qualitative descriptive study to understand perceptions of
feeling supported, identify the perceived sources, and comprehend what they classify as a
meaningful social support experience. The study showed that even when a priest has an
extensive network of social support available, it was perceived only as supplemental and
did not adequately compensate for occupational stressors. The researchers also found that
lack of intimacy and family, role expectations, and the instability of social support
sources as a result of mandatory transfers to be additional occupational stressors (Bricker
& Fleischer, 1993). The qualitative results of this study indicated that even if social
support is available from different sources throughout their social network, priests still
struggle with their perceptions of social support.

36
A study by Lee and Fung (2023) investigated the relationships between work-
family conflict (WFC), psychological distress, and well-being in Taiwanese clergy. The
sample consisted of 336 clergy members with a mean age of 46.1 years. The study
examined the four types of WFC (time-based work interference with family, time-based
family interference with work, strain-based work interference with family, and strain-
based family interference with work) and their associations with psychological distress
and well-being (life satisfaction, flourishing, and spiritual well-being). The results
showed that all four types of WFC were positively associated with psychological distress
and negatively associated with well-being. However, when modeled simultaneously, only
strain-based WFC was related to the outcomes. Furthermore, demographic factors such as
younger age, female gender, single status, working alone, and earning below the median
income were associated with higher levels of psychological distress and lower levels of
well-being (Lee & Fung, 2023). The study emphasizes the importance of stress-
management strategies among clergy to protect against burnout and promote positive
well-being. The authors suggest that structural interventions such as mentorship
programs, clergy support systems, and awareness of burnout and mental health needs can
be effective in promoting clergy mental health (Lee & Fung, 2023).
Somatic Symptoms and Health Among Clergy
A variety of studies have focused on the factors that affect the health of clergy
population. The focus of this section is on discussing studies that have been conducted on
elements of clergy life that affects their health. The section reviews somatic symptoms
and the influence they have on health. Somatic symptoms have been described as

37
discomforts such as headache, neck pain, chest pain, low back pain, and gastrointestinal
experienced by patients (Tsai, 2010). The presence of somatic symptoms has also been
described as somatization or somatic symptom disorder (D’Souza & Hooten, 2021).
Somatic symptoms have also been linked with the development of poor physical and
mental health outcomes such as cardiac dysfunction, pain, and other somatic health
complaints among patients (Penninx et al., 2013).
Proeschold-Bell and LeGrand (2012) conducted a quantitative study to examine
the physical health functioning (also known as health-related quality of life) among
United Methodist clergy compared to nonclergy population. The data collected in the
study showed that clergy exhibit significantly higher rates of chronic diseases in
comparison to their nonclergy counterparts. Such diseases include cancer, diabetes,
cardiovascular disease, and obesity. The rate of obesity among clergy aged between 35
and 64 years old was 39.7%, more than 10.3% greater than for their nonclergy
counterparts. This was attributed to work-related stress that worsened chronic illnesses.
For instance, the sample of clergy in the United Methodist church self-reported rates of
hypertension, arthritis, asthma, diabetes, and obesity; these were higher than the average
national rate. Health interventions are urgently needed to handle actual health outcomes
among clergy who are at risk of developing cancer, obesity, diabetes, and cardiovascular
diseases (Proeschold-Bell & LeGrand, 2012).
Webb et al. (2013) conducted a study to examine factors related to obesity among
the clergy (N=844), while controlling for physical activity and fruit and vegetable
consumption. Results showed that the clergy experienced a variety of chronic diseases,

38
with hypercholesterolemia (30%) and hypertension (29%) being the most common
diseases reported. The BMI measure of the clergy placed them into the obese (11%) and
overweight (38%) categories. These findings were comparable to those of the study by
Proeschold-Bell and LeGrand (2010) which used self-reported data from United
Methodist clergy to examine the prevalence of obesity among the clergy population
compared to nonclergy counterparts. The sample comprised 95% (N = 1726) of all
actively serving United Methodist clergy in North Carolina who completed the
Behavioral Risk Factor Surveillance Survey as well as self-reported weight and height
items.
The calculations of the BMI categories as well as the diagnosis prevalence rates
showed that the rate of obesity among clergy aged 35–64 years was 39.7% higher
compared to nonclergy counterparts. Further, the clergy population had higher diagnostic
rates for asthma, angina, high blood pressure, arthritis, and diabetes compared to the
nonclergy counterparts (Proeschold-Bell & LeGrand, 2010;Tice et al., 2021). The clergy
in the studie by Proeschold-Bell and LeGrand (2010) had a higher prevalence of obesity
compared to the national average (33%). The incidence of hypercholesterolemia shown in
Proeschold-Bell and LeGrand (2010) is alarming because it was twice the national
average (15%). A recent study examining the incidence of COVID-19 among priests
revealed that 39.8% of clergy were overweight, 52.2% were considered obese, 27.1%
were using anti-hypertensive medication, 23.5% were being treated for diabetes, 26.5%
were being treated for dyslipidemia, and 9.6% had a history of coronary artery disease
(Henein et al., 2021).

39
Harmon et al. (2021) explored the opportunities and resources for developing an
effective obesity-related program for clergy and their spouses. Qualitative methods,
including focus groups with 32 participants, were used to explore program targets,
opportunities and barriers that influence health behaviors, and empowering and culturally
relevant health promotion strategies. The study found that clergy health is a complex
issue influenced by various factors such as time constraints, traditions, and stress.
Participants reported struggling with stress, citing long work hours and emotional
demands as contributing factors. As discussed by Harmon et al. (2021), church traditions
can be a barrier to healthy behaviors among clergy and their spouses. Participants in the
study reported that the demands of their role as spiritual leaders often lead to neglect of
their personal health, including diet and exercise. Participants emphasized the need for
social support, particularly from peers who are going through similar experiences, and
spousal support, given the shared meals and lifestyles of spouses. The study findings
suggested that obesity-related programs should target the unique needs of both clergy and
spouses, focusing on healthy eating and personal connections, regardless of the modality
used. The study provides valuable insights into the challenges faced by clergy and their
spouses in adopting healthy behaviors and highlights the importance of tailored
interventions to address these challenges. The study highlight the complex factors that
influence clergy health, including time constraints, church traditions, and stress, and the
need for tailored interventions that address the specific needs of this population (Harmon
et al., 2021). Overall, the study underscores the importance of social support, spousal

40
support, and stress management tools in promoting healthy behaviors among clergy and
their spouses.
Adams et al. (2017) conducted a review of the quantitative literature, comparing
rates of burnout between clergy and other helping professions (e.g., social workers,
counselors, teachers, emergency personnel, and police). A total of 84 studies were used to
compare the score ranges of burnout among clergy (16 studies), social workers (13
studies), counselors (16 studies), teachers (22 studies), emergency personnel (7 studies),
police (10 studies), and MBI published mean norms. Compared to U.S. norms, the clergy
displayed moderate rates of burnout. There were three different aspects of burnout
studied in which the clergy had lower levels of burnout than police and emergency
personnel, comparable to social workers and teachers, and lower than counselors. The
three aspects of burnout measured using the Maslach Burnout Inventory were emotional
exhaustion, depersonalization, and personal accomplishment, with the clergy scoring
worse than professionals who worked as counselors. The researchers found that excessive
work expectations, excessive schedule demands, low social support, complicated
parishioners, and on-call shifts are external and systemic factors that promoted clergy
burnout.
Knox et al. (2002) analyzed data from a sample of 262 Roman Catholic clergy
residing in the United States to investigate the incidence of depression and anxiety
compared to a nonclergy sample. The results showed that depression levels among priests
in the diocese were seven times higher than the nonclergy. Additionally, rates of state
anxiety and trait anxiety were five to seven times greater than the general population. The

41
data also showed that low vocational satisfaction was a predictor of depression and low
social support was a predictor of trait anxiety. The sample of Catholic priests living with
other members of the clergy experienced moderate degrees of social support and were
satisfied with their vocation. The Catholic clergy who reported the highest degree of
burnout and depression reported lack of social support and sense of isolation as the key
contributing factors (Knox et al., 2002). According to the findings of other research, the
percentage of clergy who experience burnout might reach as high as 45% in some nations
(Jackson-Jordan, 2013). This is caused by the nature of their job as they are frequently
exposed to highly distressing news and situations in the course of discharging their duties
such as death of a member or a member’s loved one, distressed marriages, hospitalization
of a member and other forms of traumatic experiences (Proeschold-Bell et al., 2013).
A study was conducted on a sample of clergy in Florida to investigate
occupational distress, social support, mental health, and spiritual completeness using the
Patient Health Questionnaire (PHQ-9), the Clergy Occupational Distress Index (CODI),
and the Social Support Questionnaire Short Form (SSQ6) (Shaw et al., 2021). The entire
sample (N = 93) consisted of active clergy in Florida who were at least 18 years old and
not retired. The results of the study revealed that clergy had a depression rate of 12.9%,
which is worse than the previously self-reported rate of 11.1% among United Methodist
clergy study participants and the published national average for 2017 of 7.9%, as reported
by the CDC (National Institute of Mental Health, 2019; Proeschold-Bell et al., 2013;
Shaw et al., 2021). In addition, the research sample had greater occupational distress rates
than the published national mean averages. An inverse correlation was also show

42
between the SSQ6 and the PHQ-9 scores, such that higher levels of social support
available from greater numbers of sources were related to lower levels of depression
(Shaw et al., 2021). This adds to the limited body of evidence regarding the significance
of social support on the psychological well-being of clergy. A negative correlation
between years of ministry experience and PHQ-9 scores was also found (Shaw et al.,
2021). This indicates that those who have served in ministry for fewer years report higher
levels of depression than those who have served longer. This contradicts the findings of
prior studies, which revealed that longer amounts of time spent in ministry were
associated with greater levels of depression and anxiety (Proeschold-Bell et al., 2013;
Shaw et al., 2021).
Webb and Chase (2019) examined the association between occupational distress,
physical and mental health, and health behaviors among Christian clergy. The study
collected data from a convenience sample of 221 full-time clergy members who
completed a questionnaire comprising the Clergy Occupational Distress Index (CODI),
demographic, occupational, health, and behavioral variables. The study demonstrated that
elevated CODI scores were significantly associated with an increased risk of negative
health outcomes such as high blood pressure, diabetes, chronic stress disorder,
depression, anxiety, prolonged sitting time, and longer working hours per week.
Furthermore, the study suggested that occupational distress might negatively affect the
health of full-time Christian clergy, particularly those who are younger, and advocated
for further research on the temporal relationships among occupational distress, health,
and health behaviors among full-time clergy. In addition, the study revealed that found

43
that a significant proportion of clergy reported having chronic diseases such as high
blood pressure (33.5%), high cholesterol (29.0%), arthritis (15.4%), depression (14.9%),
anxiety (12.7%), and over half of the clergy were classified as obese. Logistic regression
models demonstrated that increasing age, BMI, and occupational distress were associated
with an increased likelihood of reporting a diagnosis of high blood pressure, high
cholesterol, type 2 diabetes, and arthritis. These findings suggested that the clergy might
be at a higher risk of negative health outcomes. Occupational distress was measured by
the CODI scale, with an average score of 11.5 (SD = 3.41), and the study found that
hours worked per week was a significant predictor of higher CODI scores, after
controlling for age and gender (Webb & Chase, 2019). logistic regression models
examining the effects of occupational distress on various health outcomes found that
increasing occupational distress was associated with an increased likelihood of reporting
a diagnosis of high blood pressure, type 2 diabetes, arthritis, and depression (Webb &
Chase, 2019).
Summary and Conclusions
While literature specific to Catholic clergy is limited, the literature from existing
studies suggests that this population experiences higher occupational stress, lower
perceived social support, and higher rates of chronic diseases compared to their
nonclergy counterparts. Being a preacher, pastor, teacher, administrator, counselor, and
organizer are some of the most common roles that involve highly diverse competencies
with numerous stressors. This chapter presented theories related to stress, social support,
and health. Different types of social support, including perceived organizational support

44
and perceived supervisor support, and how they reduce occupational stress and stressors
were also covered. Literature concerning the assessment of the relationship between
stress and its effects on health was also examined. The actual health outcome of clergy is
directly impacted by stress. Literature also shows a relationship between stress and
somatic symptoms, which can be indicators of poorer physical health status. Furthermore,
the extent to which perceived social support moderates the relationship between job-
related stress and somatic health symptoms among clergy has not been studied. Chapter 3
provides information on the research design and rationale, population, sampling,
recruitment, participation, and data collection procedures, threats to validity, and ethical
procedures.

45
Chapter 3: Research Method
Introduction
The purpose of this quantitative study was to determine the extent to which
perceived supervisor support and perceived organizational support moderate the
relationship between occupational distress (IV) and somatic symptoms (DV) among
Catholic clergy. In Chapter 3, I discuss the research design and rationale, population,
sampling and sampling procedures, procedures for recruitment, participation, data
collection, instrumentation and operationalization of constructs, threats to validity, and
ethical procedures.
Research Design and Rationale
This quantitative nonexperimental correlational study examined the extent to
which perceived supervisor support and perceived organizational support moderate the
relationship between occupational distress (IV) and somatic symptoms (DV) among
clergy. A correlational design was appropriate for this nonexperimental study to assess
and determine if a statistical relationship between the variables exists (Curtis et al., 2016).
A correlational design is a form of quantitative research consisting of the evaluation of
potential relationships between different variables. Therefore, the use of a correlational
design allows the use of scientific methods where different constructs are measured using
numbers to enhance the understanding of various phenomena.
For this study, occupational distress was the independent variable, somatic
symptoms was the dependent variable, and perceived supervisor support and perceived

46
organizational support were the moderators. A quantitative, nonexperimental approach
was used. Standard multiple regression analysis was used to analyze the data.
Methodology
Population
The population included priests of the Catholic church working in the United
States. For the purpose of this study, a priest were defined as a member of the clergy
ordained to the sacerdotal or pastoral office by the Catholic church. In 2020, there were
approximately 35,513 priests in the United States (Center for Applied Research in the
Apostolate [CARA], 2021). In the last 50 years, the total number of priests in the United
States decreased by 40%, from 59,192 in 1970 to 35,513 in 2020 (CARA, 2021; Lingier
& Vandewiele, 2021).
Sampling and Sampling Procedures
Convenience sampling, which is a nonprobability sampling technique, was the
sampling technique used to select the participants for this study. Participants were
recruited from various Facebook groups. The inclusion criteria for participation required
(a) the minimum age of 27, (b) being ordained as a priest by the Catholic church, (c)
having at least 2 years of experience as a priest, and (d) currently living in the United
States for a minimum of 3 years. The minimum age to participate was 27 because a
person needed at least 25 years of age to be ordained, and the inclusion criteria required 2
years of experience.
The recommended minimum sample size was determined using G*Power 3.1.9.7
software (Faul et al., 2009). The following parameters were used: an alpha level of .05,

47
five predictor variables, an anticipated effect size of .15, and statistical power of .80 to
determine the minimum recommended sample size. A medium effect size has been
reported in recent studies looking at the relationship between occupational stress and
illness or disease among clergy (Proeschold-Bell & LeGrand, 2012). However,
moderations tend to have small effect sizes, so an effect size of .05 was used for the
moderators. The five predictor variables were occupational distress, perceived supervisor
support, perceived organizational support, and the interaction variables (supervisor
support and occupational distress, organizational support and organizational support).
The results of the power analysis indicated a recommended sample size of 196
participants.
Procedures for Recruitment, Participation, and Data Collection
After the study was approved by the Walden Institutional Review Board (IRB),
participants were recruited from various public Facebook groups and individual clergy
members were contacted via email using addresses obtained from the 2022 Official
Catholic Directory. A recruitment post was made with the approval of the group
administrator that provided an explanation of the study and a hyperlink to the survey
hosted by Microsoft Forms. This same hyperlink was included in the recruitment email.
Before accessing the online survey, participants were directed to an informed consent
form that required their consent. The purpose of the study, disclosure for voluntary
participation, and the ethical considerations related to the present study were included in
the informed consent. Participants were also informed that they could withdraw their data
at any point throughout the survey, providing them with the opportunity to discontinue

48
for any reason. To maintain data integrity, all survey questions had a validation feature,
requiring participants to respond to every question to prevent missing data.
Instrumentation and Operationalization of Constructs
Clergy Occupational Distress Index
Occupational distress was measured with the Clergy Occupational Distress Index
(CODI; Frenk et al., 2013). The CODI is a five-item index designed to measure the
participant's occupational distress by assessing their perceptions of their occupational
demands and how often they have experienced a stressful situation over the past year due
to their occupation (Frenk et al., 2013). The 5-items measure the adverse impact that
occupational distress has on the health, career, and the quality of the clergy's
congregational work (Frenk et al., 2013). The five items include the following: "During
the past year, how often have the people in your congregation made too many demands of
you?"; "During the past year, how often have the people in your congregation been
critical of you and the things you have done?"; "Looking back over the past year, how
often have you experienced stress as a result of dealing with congregational members
who are critical of you?"; "Over the past year, how often have you felt lonely or isolated
in your work?"; and "Over the past year, how often have you experienced stress because
of the challenges you have in this congregation?" Participants respond to each item using
a 4-point Likert scale: 1 = never, 2 = once in a while, 3 = fairly often, and 4 = very often
(Frenk et al., 2013). The total score could range from 5 to 20.
Reliability and Validity. In the study conducted by Frenk et al. (2013), the
reliability and validity of the CODI was assessed by using the data from two samples of

49
data. The data used came from a nationally representative sample of clergy (Pulpit and
Pew National Survey of Pastoral Leaders) and a sample of clergy from nine Protestant
denominations (Church Benefits Association; Frenk et al., 2013). Specifically, the
nationally representative sample was used for construct validity assessment. A high
internal consistency was observed in two samples with Cronbach's alpha values of 0.77 in
the Pulpit and Pew sample and 0.82 in the Church Benefits Association sample (Frenk et
al., 2013).
Construct validity was assessed by examining the relationship between scores on
the CODI and symptoms of depression experienced during the previous 4 weeks (Frenk
et al., 2013). An ordinary least squares (OLS) regression model was used to achieve this.
The OLS regression model allowed the authors to evaluate the statistical association
between the dependent variable and the a measure of depressive mood during the last 4
weeks, while controlling for demographic, ministerial, and health variables (Frenk et al.,
2013). The OLS regression model's results show that there was a significant and positive
association between the CODI and depressive symptoms with a robust coefficient (p <
0.001; Frenk et al., 2013). Occupational distress was a significant predictor of depressive
symptoms. The authors conducted the exploratory factor analysis on the CODI items of
demand, criticism, stress from criticism, loneliness, and stress from challenges on each of
the two samples. In the Pulpit and Pew sample, the eigenvalues for the single factor for
occupational distress for the five items ranged from 0.65 to 0.81 (Frenk et al., 2013). For
the Church Benefits Association samples, eigenvalues for the single factor for
occupational distress for the five items ranged from 0.67 to 0.84 (Frenk et al., 2013). The

50
factor analysis demonstrated construct validity for the five items resulting in a single
factor or total score of clergy occupational distress.
Physical Health Questionnaire
Somatic symptoms were measured with the Physical Health Questionnaire (PHQ-
14; Schat et al., 2005). The PHQ-14 is a revised 14-item index (originally 32 items)
designed to measure somatic symptoms (Schat et al., 2005). The scale is composed of 14
items relating to how frequently participants experience sleep disturbances, headaches,
respiratory problems, and gastrointestinal problems, each of which is a subscale of the
PHQ-14 (Schat et al., 2005). The frequency of somatic health issues among participants
is measured by the PHQ-14, which allows for analysis using its individual subscales or a
singular overall somatic health index (Schat & Kelloway, 2003). Example items include
"How often have you had difficulty getting to sleep at night?" and "How often have you
suffered from an upset stomach (indigestion)?" Eleven of the items are answered using a
Likert-type rating, ranging from 1 (not at all) to 7 (all of the time). For the other three,
two are answered using a range of 0 to 7+ times, and one is answered using a range of 1
day to 7 days. Before analyzing the data, all items need to be reverse coded except Item 4
so that a greater mean score will reflect greater somatic health problems (Schat et al.,
2005).
Reliability and Validity. Schat et al. (2005) conducted several studies to examine
the psychometric properties of the PHQ. The first study used a sample of 194 staff
members from a hospital in Ontario to provide an initial assessment of validity by
performing exploratory factor analysis on the PHQ items (Schat et al., 2005). It was

51
confirmed that the PHQ is a psychometrically sound instrument with revealed
Cronbach’s alpha of .83, .88, .80, and .66 for each of the subscales (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections; Schat et al., 2005).
Schat et al. (2005) evaluated measurement invariance and offered tests to provide
evidence of the construct validity of the four subscales of the PHQ (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections). Principal components
extraction with varimax rotation was performed, and four factors were extracted
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections) that
cumulatively explained 68.9% of the item variance (Schat et al., 2005).
The four items that measure the frequency of sleep disturbance had eigenvalues
ranging from .56 to .85 (Schat et al., 2005). The three items that measure the frequency of
headaches had eigenvalues that ranged from .82 to .89 (Schat et al., 2005). The four items
that measure the frequency of gastrointestinal problems had eigenvalues that ranged from
.63 to .90 (Schat et al., 2005). Finally, the three items that measure the frequency of
respiratory infections had eigenvalues ranging from .72 to .79 (Schat et al., 2005).
Evidence for convergent validity was supported by the standardized parameter estimates
representing the association between negative affect (predictor variable) and the PHQ
subscales scores (outcome variable; Schat et al., 2005). The scores for negative affect
were a significant predictor for sleep disturbance (β = .47), headaches (β = .33),
gastrointestinal problems (β = .38), and respiratory illness (β = .39; Schat et al., 2005).
Schat et al. (2005) assessed discriminant validity by looking at the relationship
between PHQ subscale scores and job performance with two samples of participants. The

52
correlations between PHQ and job performance for the two samples were .10 and .002 for
gastrointestinal problems, .06 and .04 for headaches, .05 and .001 for sleep disturbance,
and .09 and .12 for respiratory infections (Schat et al., 2005). The PHQ demonstrated
discriminant validity due to the lack of significant correlations. Schat et al. (2005)
identified the internal consistency reliability for the four PHQ subscales using Sample 1
and 2 and obtaining the Cronbach’s alpha values of .84 and .86 for the gastrointestinal
problems subscale, .84 and .86 for the headaches subscale, .79 and .84 for the sleep
disturbance subscale, and .66 and .61 for the respiratory infections subscale.
Survey of Perceived Organizational Support
Perceived organizational support was measured with the Survey of Perceived
Organizational Support (SPOS), a revised eight-item index (originally 36 items) designed
and modified by Eisenberger and others (Eisenberger et al., 1986; Shanock &
Eisenberger, 2006). The initial SPOS contained 36 items with a Cronbach’s alpha of α =
.97 (Eisenberger et al., 1986). However, a shorter eight-item version of the scale was
developed following the recommendations of Rhoades and Eisenberger (2002). The
original 36-item scale was unidimensional and had high internal reliability; a meta-
analysis of existing research literature that used the SPOS found no issues if the shorter
version was used (Eisenberger et al., 2002). Example items include "The organization
values my contribution to its well-being” and "The organization appreciates any extra
effort from me” (Eisenberger et al., 1986, 2002). The eight items of the scale are
answered using a 7-point Likert-type response, ranging from 0 (strongly disagree) to 6

53
(strongly agree; Eisenberger et al., 1986, 2002). The SPOS was designed to provide a
total perceived organizational status score.
Reliability and Validity. Internal consistency was reported for the original 36-
item scale with a reliability coefficient (Cronbach's alpha) of .97 (Eisenberger et al.,
1986). Rhoades and Eisenberger (2002) conducted a meta-analysis of 73 independent
studies from different industries and found a high internal reliability for SPOS (average
Cronbach's alpha of .90). Eisenberger (2002) assessed the reliability and validity of the
eight-item version of the SPOS, which was used in the present study, using the data from
two samples of data. The data used came from a sample that consisted of 314 alumni of a
Belgian university that took part of three studies assessing the relationships among
employees’ perception of supervisor support (PSS), perceived organizational support
(POS), and employee turnover (Eisenberger et al., 2002). A high internal consistency was
observed at two different times, with Cronbach's alpha values of 0.74 at Time 1 and 0.75
at Time 2 (Eisenberger et al., 2002). The eight-item version of the SPOS was previously
used by Worley et al. (2009) in a study that involved 450 U.S. community college
employees. It was also used by Mansoor et al. (2010) in a study that involved bank
employees. It was also used by Bailey (2014) in a study that focused on hospital staff.
The study by Worley et al. showed adequate internal reliability consistency with an alpha
reliability coefficient of 0.93. The study by Mansoor et al. (2010) revealed an alpha
reliability coefficient of 0.96. Bailey achieved an internal coefficient of 0.91.
Kurtessis et al. (2017) conducted a meta-analytic evaluation that included 492
papers containing 558 research studies focused on organizational support. In his meta-

54
analysis, the SPOS had a convergent validity with affective commitment (r = .42, p <
.001), organizational identification (r = .44, p < .001), and intention to stay in
organization (r = .48, p < .001).
Survey of Perceived Supervisory Support
Supervisor support was measured with the Survey of Perceived Supervisor
Support (Shanock & Eisenberger, 2006). The Survey of Perceived Supervisor Support is
an eight-item scale that measures perceived supervisor support using a 7-point Likert-
type response format, ranging from 0 (strongly disagree) to 6 (strongly agree). This
survey was developed following Shanock and Eisenberger's recommendations to use the
SPOS and replace the word "organization" with "supervisor" (Eisenberger et al., 2002;
Shanock & Eisenberger, 2006). The survey items include statements such as "The
supervisor values my contribution to its well-being" and "The supervisor appreciates any
extra effort from me.” The eight items of the scale are answered using a 7-point Likert-
type response format, ranging from 0 (strongly disagree) to 6 (strongly agree)
(Eisenberger et al., 1986, 2002). It provides a total score that ranges from 0 to 56.
Reliability and Validity. Eisenberger (2002) assessed the reliability and validity
of the eight-item version of the SPSS, which was used in the present study, using the data
from two samples of data. The data used came from a sample that consisted of 314
alumni of a Belgian university which took part of three studies assessing the relationships
among employees’ perception of supervisor support (PSS), perceived organizational
support (POS), and employee turnover (Eisenberger et al., 2002). A high internal
consistency was observed at two different times, with Cronbach's alpha values of 0.81 at

55
Time 1 and 0.82 at Time 2 (Eisenberger et al., 2002). Several researchers have also used
this scale and found it to be reliable, with a Cronbach's alpha ranging from .93 to .95
(Igbaria & Wormley, 1992; Jayaweera, 2010; Kurlansik & Maffei, 2016). The eight-item
version of the modified Survey of Perceived Supervisor Support exhibited high internal
consistency with a Cronbach's alpha of .91 for nursing supervisors and .948 for school
supervisors (Sharma et al., 2021).
The authors examined the factor loading estimates and found that not all loadings
were highly significant for this study. As suggested by Hair (2009), to obtain convergent
validity factor loadings need to at least be .5 but preferably.7. Once the highly significant
items were adjusted, the moderate fit to the data was: χ2 (59) = 95.95, p <.05, CFI =.98,
RMSEA =.05. This enabled the researchers to establish convergent validity since the
factor loadings of all items were all higher than.7, were statistically significant (p <.05),
and all the average variance extracted (AVE) estimates were higher than the
recommended value of .5 (Bagozzi & Yi, 1988).
Research Questions and Hypotheses
RQ1: To what extent does occupational distress, as measured by the Clergy
Occupational Distress Index, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H01: Occupational distress is not a significant predictor of somatic health
symptoms (gastrointestinal problems, headaches, sleep disturbance, and respiratory
infections).

56
H1: Occupational distress is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ2: To what extent does supervisor support, as measured by the Survey of
Perceived Supervisor Support, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H02: Supervisor support is not a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
H1: Supervisor support is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ3: To what extent does organizational support, as measured by the Survey of
Perceived Supervisor Support, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H03: Organizational support is not a significant predictor of somatic health
symptoms (gastrointestinal problems, headaches, sleep disturbance, and respiratory
infections).
H3: Organizational support is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ4: To what extent does supervisor support moderate the relationship between
occupational distress and somatic health symptoms (gastrointestinal problems, headaches,

57
sleep disturbance, and respiratory infections) among Catholic clergy working in the
United States?
H04: Supervisor support does not moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
H4: Supervisor support does moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
RQ5: To what extent does organizational support moderate the relationship
between occupational distress and somatic health symptoms (gastrointestinal problems,
headaches, sleep disturbance, and respiratory infections) among Catholic clergy working
in the United States?
H05: Organizational support does not moderate the relationship between
occupational distress and somatic health symptoms (gastrointestinal problems, headaches,
sleep disturbance, and respiratory infections).
H5: Organizational support does moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
Data Analysis Plan
The data was uploaded and analyzed using the Statistical Package for Social
Sciences (SPSS) version 27.0 software. Standard multiple regression analysis was used to
determine the extent to which perceived supervisor support and perceived organizational

58
support moderate the relationship between occupational distress and somatic symptoms
among Catholic clergy. To test the moderating relationship, an interaction variable was
created by combining occupational distress with perceived supervisor support and
perceived organizational support (independent variable x moderator variables).
Subsequently, somatic symptoms (dependent variable) was regressed on the independent
variable and the interaction variables (occupational distress, perceived supervisor support
and perceived organizational support). A standard multiple regression analysis was
conducted to examine the overall impact of these variables on somatic health symptoms.
SPSS was used to evaluate all multiple regression assumptions, including
normality, homoscedasticity, linearity, multicollinearity, and independence of residuals.
Histograms and scatterplots were used to check normality and linearity. To test
homoscedasticity, a scatterplot of residuals was examined, and the Variance Inflation
Factor (VIF) was calculated to assess multicollinearity.
Threats to Validity
Self-selection bias was the first threat to validity due to the use of a convenience
sample. Self-selection may cause a distorted representation of the actual population
(Heckman, 2010). Since the study used convenience sampling, the generalizability of the
results may have been limited since there was a risk of selection bias (Etikan et al., 2016;
Keles et al., 2020). To avoid selection bias, participants should originate from the same
general population (Pannucci & Wilkins, 2010). Therefore, the sample was recruited
using groups from several geographic locations in the United States. Construct and
statistical conclusion validity threats were also probable. According to Creswell and

59
Creswell (2017), correlational designs may increase the probability of having construct
and statistical conclusion validity threats. The most common threats to the conclusion
validity are factors that can lead a researcher to reach an incorrect relationship between
the correlations of desired variables. Threats to statistical conclusion may arise from an
inadequate understanding of statistical procedures which leads to incorrect usage (García-
Pérez, 2012).
Ethical Considerations
Data collection commenced after receiving approval from the Walden University
Institutional Review Board (IRB approval 08-23-23-0488727). The survey was hosted on
Microsoft Forms and accessible via a hyperlink included in the recruitment posts and
emails. Before beginning the survey, participants read the informed consent form and had
to agree to participate by clicking the consent button, which then allowed them to
proceed to the survey. The informed consent form provided a brief description of the
study, including its purpose, procedures, risks, and benefits of participation, as well as the
voluntary nature of participation and their privacy rights. Participants were informed that
they were free to withdraw at any time without any negative consequences.
The survey was completed anonymously, with no identifying information
collected at any time, ensuring the protection of participant privacy. Participants were
encouraged to complete the survey in a private setting to ensure their responses remained
confidential. To maintain data integrity, all survey questions included a validation
feature, requiring participants to respond to every question to prevent missing data.
Participants were also informed that they had the option to withdraw their data

60
voluntarily during the survey process, allowing them to discontinue participation for any
reason.
Participants were informed that they might experience some discomfort while
completing the survey. In such cases, they were provided with a contact link to Mental
Health America (https://mhanational.org/get-help) for support and resources. This
organization offers counseling, information, referrals, and crisis intervention. Once data
collection was complete, the data was stored securely on a password-protected computer
accessible only by me. Additionally, the data was backed up on OneDrive and will be
deleted after five years in accordance with the data retention period required by the
university.
Summary
Chapter 3 presented the research design and methodology that were used in this
study. A description of the instruments that were used for data collection is provided,
along with information about their reliability and validity. The chapter also described the
recruitment process. This quantitative nonexperimental correlational study aimed to
examine the extent to which perceived social support moderates the relationship between
occupational distress (independent variable) and somatic symptoms (dependent variable)
among the Catholic clergy in the United States. Chapter 4 provides a detailed description
of the analysis and findings of the study.

61
Chapter 4: Results
Introduction
The purpose of the study was to determine the extent to which perceived
supervisor support and perceived organizational support moderate the relationship
between occupational distress and somatic symptoms among clergy. In this chapter, I
present the research questions and hypotheses, data collection procedures, evaluation of
statistical assumptions, and findings from the multiple regression analysis. Additionally,
this chapter presents the descriptive statistics of the sample and organizes the statistical
analysis results according to the following research questions:
RQ1: To what extent does occupational distress, as measured by the Clergy
Occupational Distress Index, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H01: Occupational distress is not a significant predictor of somatic health
symptoms (gastrointestinal problems, headaches, sleep disturbance, and respiratory
infections).
H1: Occupational distress is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ2: To what extent does supervisor support, as measured by the Survey of
Perceived Supervisor Support, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?

62
H02: Supervisor support is not a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
H1: Supervisor support is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ3: To what extent does organizational support, as measured by the Survey of
Perceived Supervisor Support, relate to somatic health symptoms (gastrointestinal
problems, headaches, sleep disturbance, and respiratory infections), as measured by the
Physical Health Questionnaire, among Catholic clergy working in the United States?
H03: Organizational support is not a significant predictor of somatic health
symptoms (gastrointestinal problems, headaches, sleep disturbance, and respiratory
infections).
H3: Organizational support is a significant predictor of somatic health symptoms
(gastrointestinal problems, headaches, sleep disturbance, and respiratory infections).
RQ4: To what extent does supervisor support moderate the relationship between
occupational distress and somatic health symptoms (gastrointestinal problems, headaches,
sleep disturbance, and respiratory infections) among Catholic clergy working in the
United States?
H04: Supervisor support does not moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).

63
H4: Supervisor support does moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
RQ5: To what extent does organizational support moderate the relationship
between occupational distress and somatic health symptoms (gastrointestinal problems,
headaches, sleep disturbance, and respiratory infections) among Catholic clergy working
in the United States?
H05: Organizational support does not moderate the relationship between
occupational distress and somatic health symptoms (gastrointestinal problems, headaches,
sleep disturbance, and respiratory infections).
H5: Organizational support does moderate the relationship between occupational
distress and somatic health symptoms (gastrointestinal problems, headaches, sleep
disturbance, and respiratory infections).
Data Collection
Data collection occurred exclusively online from August 26, 2023, to November
23, 2023, with approval from the Walden University Institutional Review Board (IRB
approval 08-23-23-0488727) on August 23, 2023. Catholic clergy were contacted via
administrator-approved postings in various Facebook groups. Additionally, individual
clergy members were contacted via email using addresses obtained from the 2022
Official Catholic Directory. The survey was hosted by Microsoft Forms and was
accessible through a hyperlink that was provided in the recruitment posts and emails.
Participants were required to consent to the study before proceeding with the survey, with

64
the informed consent form being the first page of the online survey. To maintain data
integrity, all survey questions had a validation feature, requiring participants to respond
to every question to prevent missing data. Furthermore, participants retained the option to
withdraw their data voluntarily during the survey process, allowing them to discontinue
participation for any reason.
Demographic Data
The participants were Catholic clergy members residing in the United States.
Each participant fulfilled the specific inclusion criteria set for the study. The inclusion
criteria for participation required (a) the minimum age of 27, (b) being ordained as a
priest by the Catholic church, (c) having at least 2 years of experience as a priest, and (d)
currently living in the United States for a minimum of 3 years. The minimum age to
participate was 27 because a person needs at least 25 years of age to be ordained and the
inclusion criteria required 2 years of experience. Participants' ages ranged from 31 to 84
years old, and their ordination duration ranged from 3 to 55 years, demonstrating a wide
range of experience levels within the priesthood. A total of 253 anonymous surveys were
completed, exceeding the recommended sample size.
Educational level varied among participants, with the majority (77.5%, n = 196)
holding a master's degree. Bachelor's degree holders constituted 6.7% (n = 17) of the
sample, while 11.9% (n = 30) possessed a doctorate or professional degree. A small
percentage of 0.4% (n = 1) had only completed high school/GED, and 3.6% (n = 9)
reported other educational backgrounds. In terms of income, the majority of participants
(59.3%, n = 150) reported an income of less than $25,000, with 34.0% (n = 86) reporting

65
an income between $25,000 and $49,999. A smaller percentage of 4.3% (n =11) reported
earning between $50,000 and $74,999, while a minority 2.4% (n = 6) did not disclose
their income. Regarding race/ethnicity, a majority of participants identified as
Caucasian/White (88.1%, n = 223). Hispanic/Latino participants represented 5.1% (n =
13), followed by Asian/Pacific Islander at 2.8% (n = 7), and African American/Black at
1.6% (n = 4). A small number did not to disclose their race/ethnicity or identified as
“Other,” each at 1.2% (n = 3). Education level, income, and race/ethnicity characteristics
for participants are presented in Table 1.
Table 1
Frequency Data for Clergy Educational Level, Income, and Race/Ethnicity
Variable
n
%
Educational level
High school/GED
1
.4
Bachelor's degree
17
6.7
Master's degree
196
77.5
Doctorate or professional degree
30
11.9
Other
9
3.6
Income
Less than $25,000
150
59.3
$25,000–$49,999
86
34
$50,000–$74,999
11
4.3
$100,000 or more
0
0
Prefer not to say
6
2.4
Race/Ethnicity
African American/Black
4
1.6
Asian/Pacific Islander
7
2.8
Hispanic/Latino
13
5.1
Caucasian/White
223
88.1
Native American/Alaskan Native
0
0
Prefer not to say
3
1.2
Other
3
1.2
Note. Due to rounding errors, percentages may not equal 100%.

66
Results
Descriptive Statistics
Descriptive statistics indicated that participants reported relatively high levels of
organizational support (M = 38.86, SD = 6.71) and supervisor support (M = 39.77, SD =
7.09). Occupational distress had a moderate mean value (M = 14.49, SD = 2.42). Somatic
symptoms had a mean score reflecting a moderate level of somatic symptoms among
participants (M = 29.08, SD = 5.96). Table 2 presents the descriptive statistics for the
study variables.
The correlation analysis revealed several significant relationships among the
study variables. Organizational support and supervisor support showed a significant
positive correlation (r = .554, p < 0.01), indicating that higher levels of organizational
support were associated with higher levels of supervisor support. Furthermore, the
correlation between organizational support and somatic symptoms was negative (r =
-.197), suggesting that higher levels of organizational support were associated with lower
levels of somatic symptoms, though this correlation was not statistically significant.
Similarly, the correlation between supervisor support and somatic symptoms was
negative (r = -.162), indicating that higher supervisor support was associated with lower
somatic symptoms, but this correlation was also not statistically significant. Occupational
distress did not show significant correlations with organizational support, supervisor
support, or somatic symptoms. The correlations were all negative but relatively small and
not statistically significant (r = -.065 with organizational support, r = -.097 with
supervisor support, and r = -.045 with somatic symptoms).

67
Table 2
Mean, Standard Deviation, and Correlations for Study Variables
M
SD
Organizational
support
Supervisor
support
Occupational
distress
Somatic symptoms
Organizational
support
38.86
6.71
.554
-.065
-.197
Supervisor
support
39.77
7.09
-.097
-.162
Occupational
distress
14.49
2.42
-.045
Somatic
symptoms
29.08
5.96
Evaluation of Statistical Assumptions
To evaluate if the data met the assumptions for a multiple regression analysis,
normality, linearity, multicollinearity, and homoscedasticity were assessed. Normality
was assessed using the Shapiro-Wilk test; results demonstrated that supervisor support,
organizational support, somatic health symptoms, and occupational distress significantly
deviated from normality. Further analysis of skewness and kurtosis values for all
variables revealed no significant asymmetry or extreme deviations from a normal
distribution. Specifically, skewness values ranged between -.218 and .599, and kurtosis
values varied from -.472 to .021, all within the acceptable limits of ±2 for skewness and
±3 for kurtosis as recommended by Westfall and Henning (2013). This indicated a
satisfactory level of normality for the variables, supporting their suitability for regression
analysis despite the slight deviations detected. These findings, including the specific tests
of normality, skewness, and kurtosis values, are detailed in Table 3.

68
Table 3
Normality Testing for Study Variables
Variable
Shapiro-Wilk
df
p
Skewness
Kurtosis
Supervisor support
.989
253
.049
-0.218
-0.446
Organizational support
.973
253
< .001
-0.403
-0.472
.
Somatic health symptoms
.968
253
< .001
0.599
0.021
Occupational distress
.980
253
.001
-0.133
-0.206
Multicollinearity among the predictor variables was evaluated using variance
inflation factor (VIF) values. The results showed elevated values suggesting a high
degree of multicollinearity among the predictor variables. To address this concern and
enhance the statistical integrity of the model, supervisor support, organizational support,
and occupational distress were centered prior to regression analysis. The centering
method was used based on recommendations from researchers on addressing
multicollinearity in regression models (Kyriazos & Poga, 2023). The centering method
effectively decreased the VIF values, ensuring that they remained below the accepted
threshold of 10. The centered VIF values for supervisor support (1.457), organizational
support (1.455), and the interactions between supervisor support and occupational
distress (1.384), as well as between organizational support and occupational distress
(1.392), were improved after the centering procedure. These adjusted values showed that
the potential multicollinearity concern was reduced, allowing each predictor to contribute
to the model independently and affirming the model's adherence to the necessary
assumptions for a comprehensive multiple regression analysis (Kyriazos & Poga, 2023).
The VIF values for occupational distress were also low (1.03), indicating that this

69
variable does not contribute to multicollinearity. The VIF values for the predictor
variables are presented in Table 4.
Table 4
Tolerance and VIF Values for the Predictor Variables
Variable
Tolerance
VIF
Occupational distress
.971
1.03
Supervisor support
.686
1.46
Organizational support
.687
1.46
Interaction (SSxOD)
.722
1.38
Interaction (OSxOD)
.718
1.39
The skewness and kurtosis values were compared against standard guidelines to
determine if the data distribution deviated from normality. The residuals of the regression
followed a normal distribution. This was confirmed by examining the normal predicted
probability (P-P) plot, which shows that the residuals conformed to the diagonal
normality line, as shown in Figure 1.

70
Figure 1
Residual Scatterplot for Homoscedasticity
To check for homoscedasticity, a residual scatterplot was analyzed. The
scatterplot indicated that the residuals were evenly distributed around the regression line,
suggesting that the variance of the residuals is constant across different levels of the
predicted values. This pattern confirmed that the assumption of homoscedasticity was
met, as shown in Figure 2.
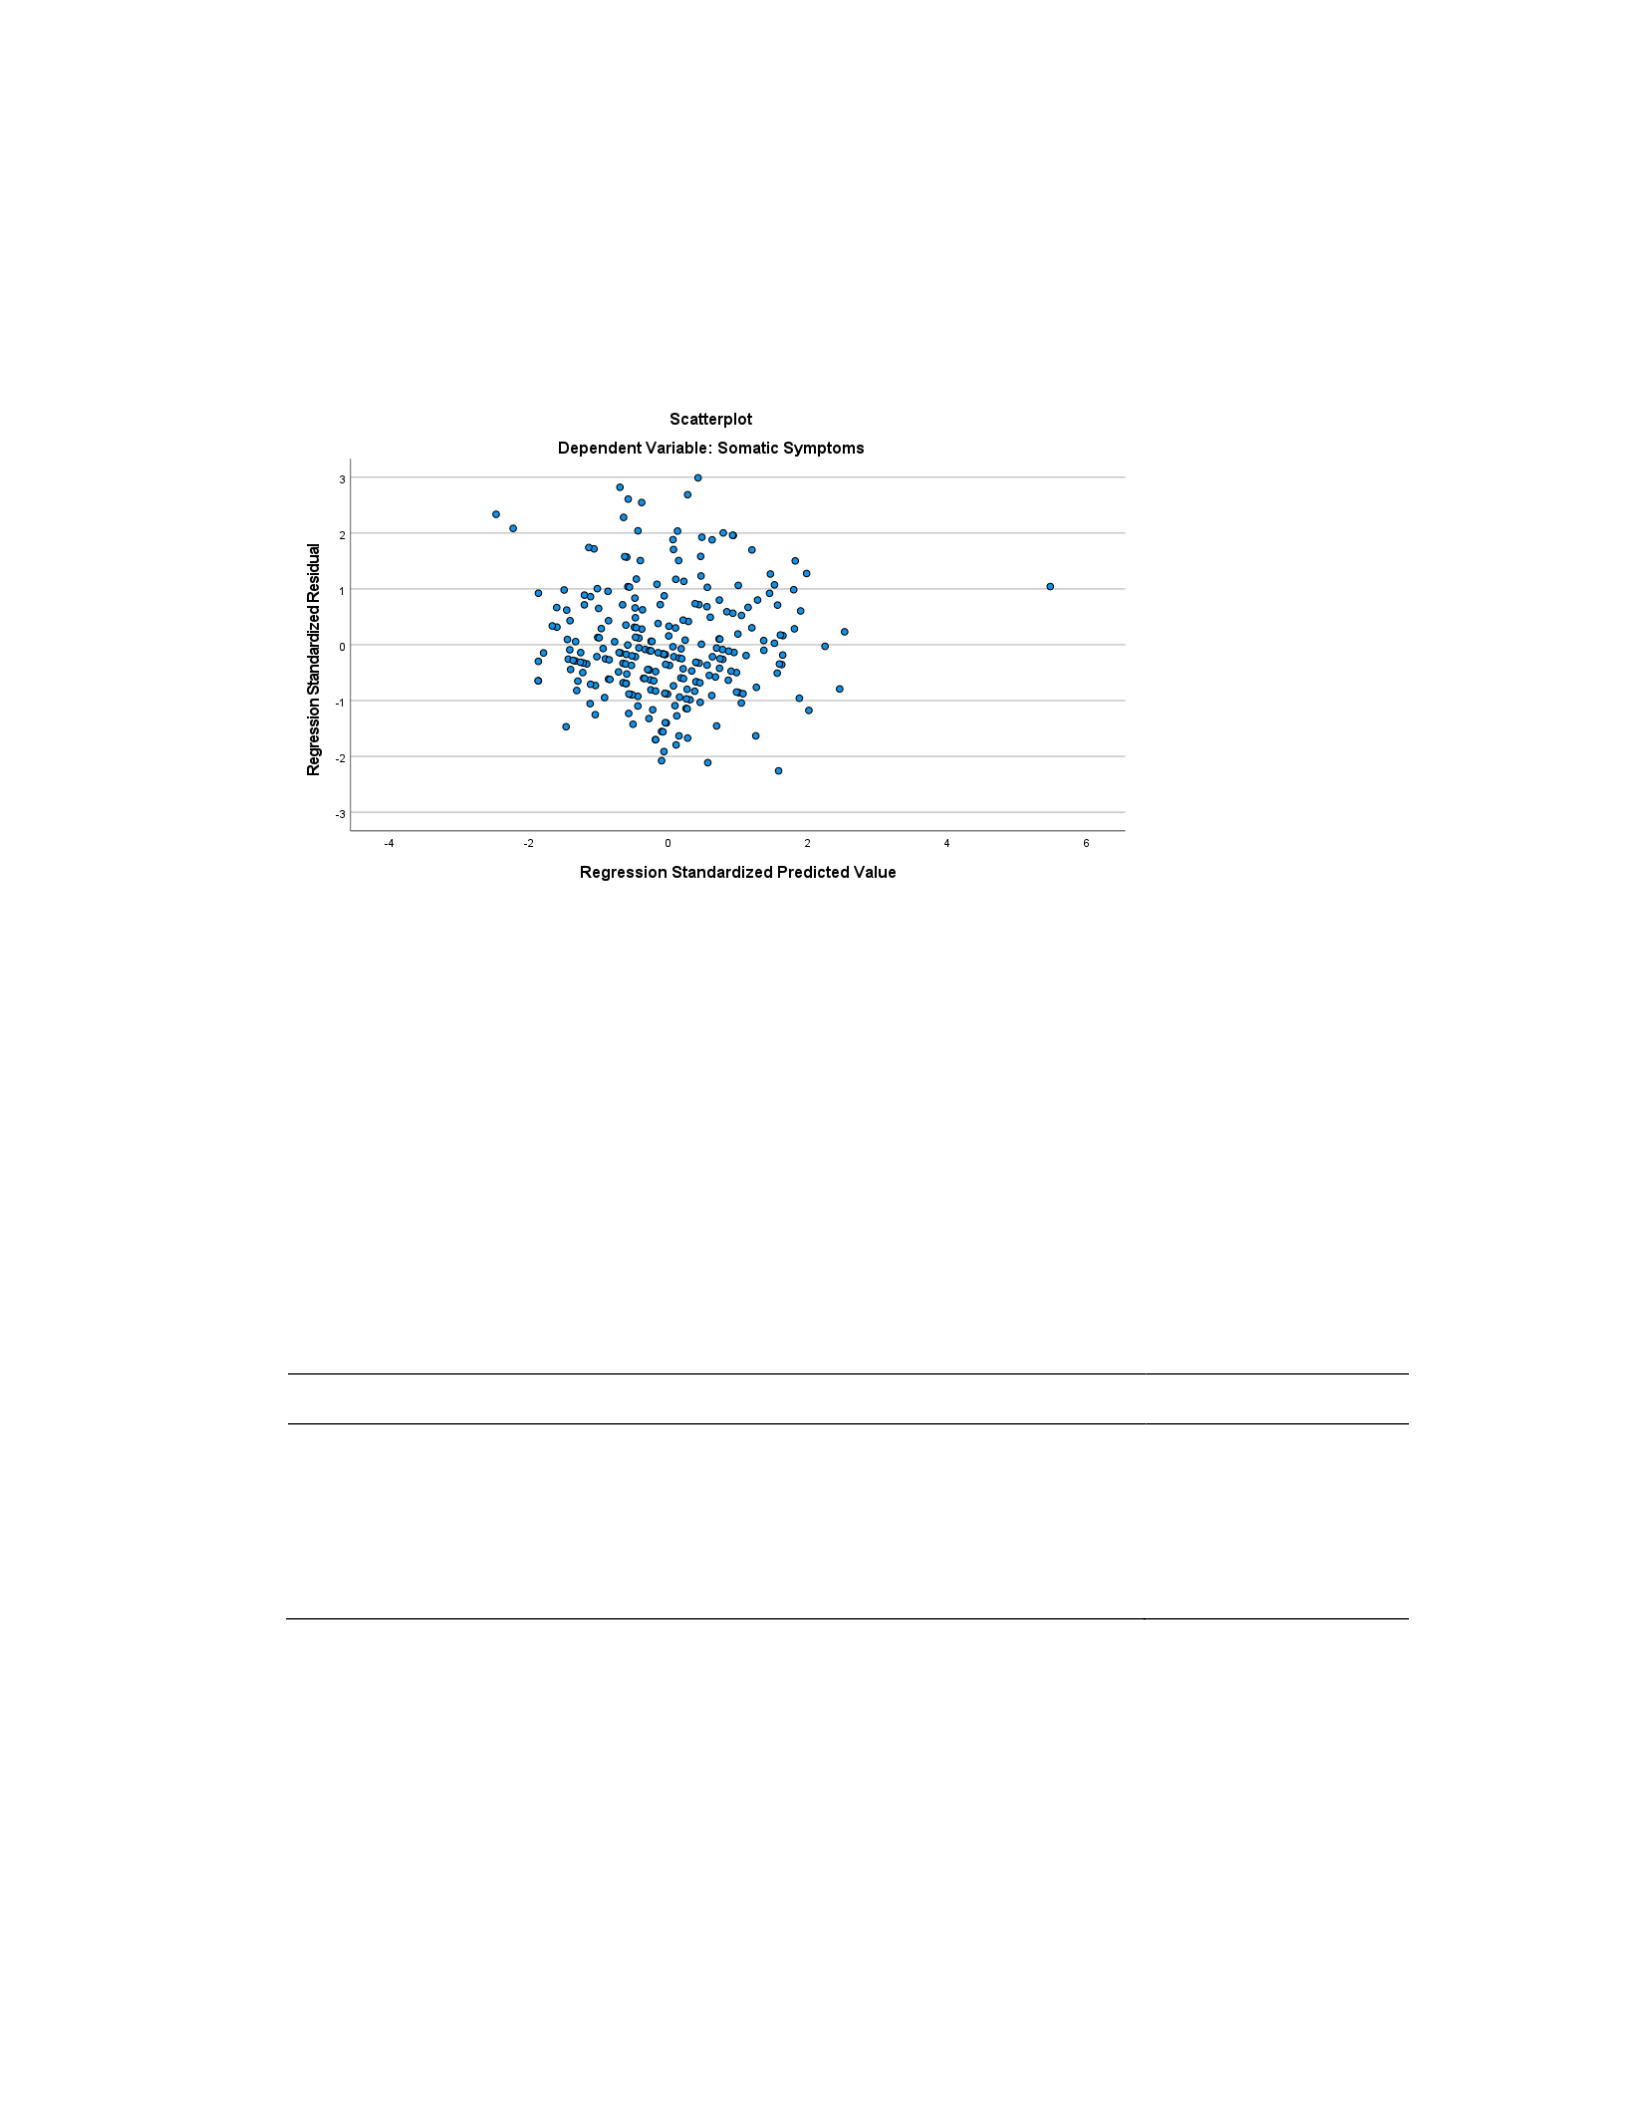
71
Figure 2
Normal Predicted Probability Plot
The reliability of the instruments utilized for the current sample was assessed by
calculating Cronbach’s alpha. Table 5 lists the Cronbach’s alpha coefficients for each
instrument, demonstrating acceptable internal consistency with values ranging between
.70 and .84.
Table 5
Cronbach’s Alpha Coefficients for Study Instruments
Instrument
α
Survey of Perceived Supervisor Support
.837
Survey of Perceived Organizational Support
.809
Patient Health Questionnaire-14
.703
Clergy Occupational Distress Index
.732
Multiple Regression Analysis
The overall multiple regression model was statistically significant, F(5, 247) =
5.043, p < .001, R = .304, R2 = .093, explaining 9.3% of variance in somatic health

72
symptoms. Examination of the regression coefficients showed that occupational distress
(b = -.231, t = -1.525, p = .129) and supervisor support (b = -.085, t = -1.383, p = .168)
were not significant predictors of somatic symptoms. Therefore, I failed to reject the null
hypotheses for research questions 1 and 2. However, organizational support was a
significant predictor of somatic symptoms (b = -.133, t = -2.050, p = .041), indicating that
higher levels of organizational support predicted lower levels of somatic symptoms.
Thus, I rejected the null hypothesis for research question 3 and accepted the alternative
hypothesis.
The moderating effects of supervisor and organizational support on the
relationship between occupational distress and somatic symptoms were significant. The
interaction between supervisor support and occupational distress was significant (b = -
0.077, t = -3.104, p = .002), as well as the interaction between organizational support and
occupational distress (b = 0.080, t = 3.047, p = .003). Because both moderation effects
were significant, I rejected the null and accepted the alternative hypotheses for research
questions 4 and 5.
The results showed that while occupational distress (b = −.231, t = −1.525, p =
.129) and supervisor support (b = −.085, t = −1.383, p = .168) alone did not significantly
predict somatic health symptoms, organizational support (b = −.133, t = −2.050, p = .041)
did have a significant negative effect, as shown in Table 6. This means that higher
organizational support was associated with fewer somatic symptoms.
Furthermore, the moderation effect of supervisor support and organizational
support was significant, indicating that they significantly moderated the effects of

73
occupational distress on somatic symptoms. Specifically, higher levels of supervisor
support (b = −0.077, t = −3.104, p =. 002) buffered the negative impact of occupational
distress on somatic symptoms, reducing somatic symptoms. However, higher
organizational support (b = 0.080, t = 3.047, p = .003) resulted in an increase of somatic
symptoms.
Table 6
Regression Coefficients for Individual Predictors and Moderators
b
SE
β
t
p
95% CI
sr2
Intercept
29.032
.362
80.155
<.001
Occupational distress
-.231
.151
-.094
-1.525
0.129
-.529
.067
.009
Supervisor support
-.085
.062
-.101
-1.383
0.168
-.261
-.005
.017
Org. support
-.133
.065
-.150
-2.050
0.041
-.207
.036
.008
Interaction (SSxOD)
-.077
.025
-.221
-3.104
0.002
-.125
-.028
.038
Interaction (OSxOD)
.080
.026
.218
3.047
0.003
.028
.132
.036
Summary
Multiple regression analysis, including moderation effects, was conducted to
determine the extent to which perceived supervisor support and perceived organizational
support moderate the relationship between occupational distress and somatic symptoms
among clergy. The findings indicated that while occupational distress and supervisor
support alone did not predict somatic health symptoms, higher levels of organizational
support predicted fewer somatic symptoms. Additionally, the moderation effects showed
that supervisor support reduced the effects of occupational distress, lowering somatic
symptoms, and organizational support increased the effects, resulting in more somatic
symptoms. Chapter 5 provides an interpretation of the findings, discusses the limitations,

74
offers recommendations for future research, and describes the implications for positive
social change.

75
Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
The purpose of this study was to examine the extent to which perceived
supervisor support and perceived organizational support moderate the relationship
between occupational distress and somatic symptoms among clergy. With a sample of
Catholic clergy, this study aimed to fill a gap in the literature regarding the health impacts
of occupational distress in this unique population. Clergy often face unique stressors due
to their roles, including emotional labor, high demands, and the need for constant
availability to their congregations, which can lead to significant health issues
(Proeschold-Bell et al., 2011).
The findings indicated that organizational support significantly predicted lower
levels of somatic symptoms. In contrast, occupational distress and supervisor support
alone did not show a significant direct effect on somatic symptoms. Significant findings
also showed that supervisor support buffered the effects of occupational distress,
reducing somatic symptoms, while organizational support increased the effects of
occupational stress, increasing somatic symptoms. In this chapter, I interpret the findings,
discuss the limitations of the study, provide recommendations for future research, and
discuss the implications for positive social change.
Interpretation of the Findings
Occupational Distress
The results indicated that occupational distress was not a significant predictor of
somatic health symptoms. This suggests that while occupational distress may be a factor

76
in the lives of clergy, it may not directly influence their physical health symptoms as
measured in this study. This finding is surprising given the extensive literature that
typically links occupational distress to various negative health outcomes. For example,
Proeschold-Bell and LeGrand (2010, 2012) emphasized the direct effects of job strain on
health, highlighting how occupational distress significantly impacts clergy's physical
health. They found that United Methodist clergy reported higher rates of obesity,
diabetes, asthma, arthritis, and high blood pressure compared to the general population.
The findings also showed that over 41% of United Methodist clergy reported obesity,
36% had high blood pressure, 34% had arthritis, 14% had asthma, and 13% had diabetes,
with these rates being significantly higher than those of their nonclergy counterparts.
Similarly, Miles and Proeschold-Bell (2013) indicated that occupational stress among
clergy is associated with higher rates of chronic disease and burnout, further establishing
the expected link between job-related stress and health outcomes.
This current result does align with other research suggesting that the impact of
stress on health can be moderated by various factors, such as individual resilience or
external support (Cohen & Wills, 1985; Ozbay et al., 2007; Proeschold-Bell et al., 2011;
Sonnentag, 2018). Other researchers have proposed that social and personal resources can
buffer the negative effects of stress, leading to less pronounced health symptoms
(Gottlieb et al., 2000). This indicates that while occupational distress alone may not be a
direct predictor of physical symptoms, the presence of moderating variables such as
sources of social support could play a crucial role in determining health outcomes. The
unique nature of clergy work and stressors may also contribute, as the demanding nature

77
of pastoral duties combined with a strong sense of vocation might lead clergy to develop
coping mechanisms that mitigate the adverse effects of stress on their physical health
(Proeschold-Bell et al., 2011). Further research is necessary to explore these moderating
factors and better understand the complex relationship between occupational distress and
health among clergy.
Supervisor Support
The results of the current study indicate that supervisor support was not a
significant predictor of somatic health symptoms. This result contrasts with much of the
existing literature, which often highlights the critical role of supervisor support in
mitigating stress-related health outcomes (Jain et al., 2013; Shanock & Eisenberger,
2006). Supervisor support has been documented to reduce stress and improve well-being
in various occupational settings by providing emotional and instrumental resources that
help employees manage work-related stressors.
This finding may be explained by the unique nature of clergy work, where support
can come from multiple sources beyond immediate supervisors. Clergy members might
receive significant support from congregational members, peers, or spiritual practices,
which could offset the influence of supervisor support alone on their health outcomes
(Miles & Proeschold-Bell, 2013). Moreover, the specific dynamics within religious
organizations might lead to different patterns of support and stress management
compared to secular workplaces. This suggests that future research should consider the
broader network of support available to clergy and its impact on their health and well-
being.

78
Organizational Support
The findings from the current study indicated that organizational support was a
significant predictor of somatic symptoms. Higher levels of organizational support were
associated with fewer somatic symptoms, highlighting the critical role that organizational
support plays in the well-being of clergy. This finding is consistent with the work of
Eisenberger et al. (1986) and Rhoades and Eisenberger (2002), who found that perceived
organizational support is crucial for employee well-being. Additionally, similar
conclusions have been drawn in studies focusing on various professional contexts,
including healthcare workers and educational settings (Ibrahim et al., 2021; Sharma et al.,
2021).
This result underscores the importance of a supportive organizational
environment in mitigating the health impacts of occupational stress. Organizational
support may provide resources, emotional support, and a sense of belonging that can
buffer the negative effects of stress, leading to better health outcomes. The findings align
with research suggesting that when employees feel valued and supported by their
organization, they are more likely to experience positive health outcomes (Eisenberger et
al., 2002). For clergy, this support can be particularly impactful given the emotionally
demanding nature of their work. Studies have also shown that effective organizational
support structures contribute to overall job satisfaction and reduced burnout rates among
employees, including those in high-stress professions (Haber et al., 2007; Sonnentag,
2018).

79
Moderating Effects of Supervisor and Organizational Support
The results from the current study showed significant moderating effects for both
supervisor support and organizational support. Both supervisor and organizational
support moderated the relationship between occupational distress and somatic symptoms.
Supervisor support had a negative moderating effect on the relationship between
occupational distress and somatic symptoms, whereas organizational support had a
positive moderating effect on the relationship between occupational distress and somatic
symptoms.
The moderating effect of supervisor support on occupational distress indicated
that higher levels of supervisor support decreased the negative effects of occupational
distress on somatic symptoms, resulting in fewer symptoms. This negative moderating
effect is consistent with previous research regarding the protecting factors of social
support against the detrimental impacts of stress on both mental and physical health.
These findings are also consistent with the stress-buffering model proposed by Cohen and
Wills (1985), which suggests that social support can protect individuals from the harmful
effects of stress. Proeschold‐Bell et al. (2015) noted that the perceived availability of
social support buffers stress levels and consequently improves well-being. Additionally,
Szkody et al. (2021) demonstrated that social support protects against the harmful effects
of stress on both mental and physical health.
The moderating effect of organizational support on occupational stress indicated
that higher levels of organizational support increased the negative effects of occupational
distress on somatic symptoms, resulting in more somatic symptoms. This positive

80
moderating relationship aligns with other studies that have shown that organizational
support needs to be carefully managed to avoid increasing stress levels due to heightened
expectations and responsibilities. For example, while perceived organizational support is
generally beneficial, a study by Xu and Yang (2021), who used the same measure of
perceived organizational support as the current study, identified that the buffering effect
of organizational support occurs only when the support received matches the coping
requirements of the stressors. They suggested that the absence of a buffering effect on
stress may be due to the measurement of general organizational support rather than
support specifically tailored to the stressors. This could explain the positive relationship
observed in my study. When organizational support does not match the employees'
specific stressors, employees may perceive the organization as responsible for their stress
and feel unsupported, which can further increase their stress and related symptoms (Xu &
Yang, 2021).
Supervisors are also frequently perceived as the personification of their
organization, and their behaviors and attitudes can significantly shape employees' views
of the organization (Zhang et al., 2020). This dual role could explain why supervisor
support appears to buffer the negative effects of occupational stress more effectively than
general organizational support. Supervisors not only provide direct support but also
represent organizational policies, which may influence how employees perceive and
receive organizational support (Haas, 2020). Additionally, the level of support provided
by supervisors can impact the implementation and effectiveness of broader organizational
support measures, suggesting that some moderating effects of organizational support are

81
mediated by the supervisor (Zhang et al., 2020). Future research should explore how
other factors could influence the moderating effects of supervisor and organizational
support.
The findings from this study support the application of the stress-buffering model,
which proposes that social support can mitigate the adverse effects of stress on health
(Cohen & Wills, 1985). The study revealed that supervisor support had a significant
negative moderating effect on the relationship between occupational distress and somatic
symptoms, aligning with the stress-buffering hypothesis. This suggests that supervisor
support can effectively reduce the negative impact of occupational distress, consistent
with previous research by Proeschold‐Bell et al. (2015) and Szkody et al. (2021).
On the other hand, the study found that organizational support increased somatic
symptoms when occupational distress was high, indicating a positive moderating
relationship. This finding suggests that while organizational support can be beneficial, it
may also contribute to increased stress levels if it does not align to the specific stressors
faced by clergy. This aligns with Liu and Onwuegbuzie (2012), who found that
organizational support needs to be carefully managed to avoid increasing stress levels.
This complex relationship underscores the need for tailored support systems that address
the specific stressors faced by clergy (Shaw et al., 2021; Zhang et al., 2020).
Limitations of the Study
The first limitation was the convenience sampling technique, which limits the
generalizability of the results. The study focused on Catholic clergy working in the
United States, limiting the findings to this specific population. Recruiting participants

82
through specific networks and online platforms may have introduced selection bias, as
those who chose to participate might differ in meaningful ways from those who did not.
Additionally, some clergy might not have access to the internet or email, limiting their
ability to participate and thereby affecting the representativeness of the sample. This
limitation means that the findings may not be generalizable to all clergy or those working
in different religious contexts or geographical regions (Eagle, 2019).
The second limitation was the use of self-reported measures, which introduces the
potential for response bias. Participants may have answered questions in a socially
desirable manner, especially given the sensitive nature of topics such as occupational
stress and somatic health symptoms. While steps were taken to ensure anonymity and
confidentiality, some participants may not have provided entirely honest responses,
which could affect the validity of the findings. Self-report data can also be influenced by
the participant's current mood or recent experiences, which may not accurately reflect
their typical state (Podsakoff et al., 2012).
The third limitation was the cross-sectional design of this study. This design
allowed for a snapshot of the current state of occupational distress, support, and health
symptoms among clergy, but it does not provide information about changes over time. To
examine how these variables interact over an extended period and to gain a better
understanding of the moderating effects of organizational support, future researchers
should consider longitudinal studies. While cross-sectional data can identify associations,
such data do not allow for the examination of changes over time (Levin, 2006).

83
The fourth limitation was the influence of external factors such as the COVID-19
pandemic. The pandemic introduced unique stressors and altered typical work
environments, which could have impacted the levels of occupational stress and support
reported by the participants. Additionally, the prevalence of COVID-19 symptoms could
have contributed to increased somatic symptoms among participants, complicating the
interpretation of the results. Studies have shown that the pandemic significantly elevated
stress levels across various sectors due to increased workloads, fear of infection, and
changes in work routines (Barello et al., 2020; Prasad et al., 2021). For example, research
on healthcare professionals in Italy indicated heightened burnout and somatic symptoms
during the pandemic (Barello et al., 2020). Furthermore, several systematic reviews of the
literature found that somatic symptoms were prevalent among patients, healthcare
workers, and the general population during the COVID-19 pandemic, often associated
with mental distress (Piao et al., 2022; Sriharan et al., 2021; Theocharis et al., 2023).
Recommendations
This study provided insights into the relationship between occupational distress,
social support, and somatic symptoms among Catholic clergy in the United States.
Further research is essential to address the limitations and enhance the understanding of
these relationships. Future studies should replicate this research with larger and more
diverse samples of clergy, including those without access to electronic means of
communication, as they may represent a population with lesser levels of support.
Expanding the sample size and diversity would improve the generalizability of the
findings. Studies have shown that occupational stress and support systems can vary

84
significantly across different cultural and organizational contexts (Dollard & Bakker,
2010; Geurts & Demerouti, 2003; Piao et al., 2022; Sriharan et al., 2021). By including a
broader range of participants, future research can provide a more comprehensive
understanding of how occupational stress and support systems impact somatic health
symptoms among clergy.
Longitudinal studies are necessary to examine the possible changes in the
relationships between social support, occupational stress, and somatic symptoms over
time. The cross-sectional design of the current study provides a snapshot of the existing
conditions but does not capture possible changes over time. Longitudinal research would
allow for the observation of how these variables interact over extended periods and could
establish causal pathways (Levin, 2006). This approach would provide a deeper
understanding of the long-term effects of occupational stress and the complex moderating
role of social support.
Future research should also explore additional factors that may influence the
relationship between occupational stress and somatic symptoms. These factors could
include personal coping strategies, social support outside the workplace, and individual
differences in stress resilience and could provide a more holistic view of the factors that
contribute to the well-being of clergy. Research has shown that personal coping
mechanisms and social support networks play a crucial role in moderating the effects of
occupational stress (Eagle et al., 2019; Miles & Proeschold-Bell, 2013; Proeschold-Bell
et al., 2013). Examining these additional factors can identify more comprehensive
strategies to support clergy health.

85
Future research should also consider the impact of external factors, such as the
COVID-19 pandemic, on clergy health. The pandemic introduced unique stressors and
altered typical work environments, which could have impacted the levels of occupational
stress and support reported by the participants (Barello et al., 2020; Prasad et al., 2021).
Additionally, the prevalence of COVID-19 symptoms could have contributed to
increased somatic symptoms among participants, complicating the interpretation of the
results. Studies have shown that the pandemic significantly elevated stress levels across
various sectors due to increased workloads, fear of infection, and changes in work
routines (Barello et al., 2020; Prasad et al., 2021).
Implications
Occupational stress remains a significant issue for clergy, impacting their overall
well-being and health. The current study investigated the relationship between perceived
supervisor and organizational support, occupational distress, and somatic symptoms
among clergy. The results from this study improve our understanding of that relationship.
The findings indicated that while supervisor support decreased the somatic symptoms
associated with occupational distress, organizational support increased these symptoms.
This stresses the importance of managing organizational support carefully and tailoring
support systems to the unique needs of clergy (Ruiz-Prada et al., 2021). The study
highlights the complexity of support systems and their moderating effects on clergy
health, emphasizing the distinct roles of supervisor and organizational support. These
insights contribute to the broader body of knowledge on clergy health, supporting the
views of Proeschold-Bell et al. (2015) and Miles and Proeschold-Bell (2013), who

86
highlight the importance of tailored support systems in mitigating stress-related health
issues among clergy. By understanding these dynamics, employers, health agencies, and
religious organizations may use the results to develop more effective social support
strategies focused on the needs of the clergy population and other high-stress occupations
that improve the overall health and well-being. This approach would be beneficial to the
clergy as well as the parishioners they serve, as occupational distress has a significant
influence on daily functioning of the clergy (Eagle et al., 2022).
Conclusion
This study examined the relationship between support systems, occupational
distress, and somatic symptoms among Catholic clergy. Clergy often take on a variety of
high-demand roles such as spiritual leaders, counselors, administrators, educators, and
caregivers (Miles & Proeschold-Bell, 2013; Proeschold-Bell et al., 2011), leading to
elevated levels of occupational stress and higher rates of stress-related health issues
compared to the general population (Miles & Proeschold-Bell, 2013; Proeschold-Bell et
al., 2011). The current findings highlight the complex dynamics of support systems,
showing both supervisor support and organizational support moderated the relationship
between occupation stress and somatic symptoms. Supervisor support was found to
decrease somatic symptoms, whereas organizational support increased somatic
symptoms. These results underscore the necessity for tailored support strategies to
effectively address the unique needs of clergy. Tailored support strategies, as suggested
by Eagle et al. (2022) and Proeschold-Bell et al. (2015), may mitigate the adverse health
impacts of occupational stress on clergy. Until this complex relationship is further

87
delineated, clergy will continue to experience higher-than-average levels of occupational
distress and associated negative health outcomes.

