


An Exploration on the Barriers to Accessing Mental Health Services Among
South Asian Youth
HPE 1005 - Mental Health Issues

Introduction
Canada’s South Asian population has been growing rapidly in the past several decades
with over a 1.5 million South Asians residing in Canada in 2016 (Bakhshaei & Henderson,
2016). With such a large population of Canadians identifying as South Asian, it is becoming
increasingly important to understand the experience of being South Asian Canadian (this includes
both South Asians born in Canada and those who immigrated to Canada). One particular area of
concern in psychological research is the mental health of South Asian Canadians. Approximately
one in five Canadians will experience mental health or substance use problems in any given year,
and by the time Canadians reach the age of 40, one in two will have experienced mental health
problems (Smetanin et al., 2011). In the last two decades, a number of studies have emerged
identifying the unique factors contributing to poor mental health for South Asians living in
Canada, including stress from the immigration process and experiences with racism and
discrimination (Inman et al., 2014). However, despite increasing concerns of mental health
problems, research shows that South Asians routinely underutilize mental health services (Karasz
et al., 2016). This may leave many South Asians with unsupported mental health problems as one
study found that South Asians have higher level of unmet mental healthcare needs compared to
White and other East/Southeast Asian groups (Gadalla, 2010).
A scan of the extant literature suggests that low service utilization can be understood as a
result of two overarching issues: 1) barriers in the mental healthcare system and 2) mental health
stigma among members of the South Asian community in Canada. Issues with how mental illness
and treatment are conceptualized in Western society result in mental health services that are often
times incompatible with South Asian conceptions of treatment or healing (Ekanayake, Ahmed, &
McKenzie, 2012). Likewise, negative experiences from service providers such as

microaggression relating to race and a lack of cultural awareness can deter help-seeking
behaviour (Inman et al., 2014; Li & Browne, 2000). Similarly, mental health stigma and its
intersection with race and culture can lead to ineffective mental health support or deter service
utilization altogether (Arora, Metz, & Carlson, 2016; Loya, Reddy, & Hinshaw, 2010). Current
research in the field has not adequately investigated the in-depth experiences of Canadian South
Asians in accessing mental health services and the barriers they may face. Notably, little research
exists on the experiences of South Asian youth (16-27 years old), especially Canadian born youth
whose experiences may differ from their immigrant counterparts (Inman et al., 2014). The
purpose of the present study is to understand the experiences of both Canadian-born and
immigrant South Asian youth living in Canada experiencing mental health problems with respect
to accessing mental health services. Investigating these experiences and situating them in the
context of structural forces of oppression including systemic racism, discrimination, and cultural
stigma are the main goals of this project.
Literature Review
A Brief History on The Arrival of South Asians in Canada
South Asian refers to the ethnic group of people who are from the Indian subcontinent
including India, Pakistan, Bangladesh, Nepal, and Sri Lanka. While these different countries may
often be lumped into a single group, South Asia comprises a diverse number of cultures,
religions, and languages (Bakhshaei & Henderson, 2016). Early South Asian settlements began
in the late 19th century when Sikhs from Punjab India arrived in British Columbia for work
(Government of Canada, n.d.). These South Asians, mainly men, arrived to work in lumber,
mining, and railway industries (Government of Canada, n.d.). However, in 1908, the
Government of Canada implemented the “continuous journey regulation” as a part of the

Immigration Act. This regulation prohibited immigrants from entering Canada unless they came
by continuous journey from their native country, in other words, if a ship made stops prior to
arriving to Canada, they were prohibited from docking in Canada (Government of Canada, n.d.).
This created barriers to South Asians as the trip from most South Asian regions to Canada
required stops (Government of Canada, n.d.). Additionally, the regulation prevented British
subjects such as those living in India from entering Canada as immigrants (Government of
Canada, n.d.). This prevented many of the men in these early Sikh communities from bringing
their families to Canada (Government of Canada, n.d.). The continuous journey regulation
remained in effect until 1947 with further racial restrictions being repealed in the following two
decades (Government of Canada, n.d.).
During the end of British rule of India in the 1940s, South Asians living in Canada were
eligible to apply for Canadian citizenship and given the rights to vote and hold office (Ghosh,
2017). Likewise, Canada’s immigration regulations became more relaxed with the hopes of
expanding the economy through a larger workforce comprised of new immigrants (Ghosh, 2017).
In 1967, Canada shifted to an immigration points system which focused on the personal, social,
and occupational characteristics of immigrants in order to accept highly skilled individuals
(Ghosh, 2017). Between 1967-1975, over 10 000 South Asians arrived in Canada, most of whom
were professionals ranked highly in the points system (Ghosh, 2017). Since then, many South
Asians have arrived in Canada, both as immigrants and refugees as a result of the 2010 refugee
reforms where Canada resettled refugees from over 140 countries (Ghosh, 2017; Government of
Canada, 2021).

Mental Health Problems Among the South Asian Diaspora
Mental health has become an increasing concern for South Asians in North America and
the United Kingdom. A study conducted by Lee, Martin, & Lee (2014) found that South Asians
living in the United States had a 24.5% lifetime rate of any diagnosed mood, anxiety, and
substance use disorder compared to East and Southeast Asians who had a lifetime rate of 22.5%
and 34.6% respectively. Likewise, an analysis of the Canadian Community Health Survey from
2011 found that approximately 11.5% of Canadian South Asians reported being diagnosed with a
mood or anxiety disorder (Islam, Khanlou, & Tamim, 2014). In comparison, 10.1% of Canadians
reported mental or substance use disorders in 2012 (Statistics Canada, 2013). There are several
factors that can contribute to poor mental health, however a particularly important factor that is
often cited in research is the migration process. Several aspects of the migration process in
Canada can create mental health problems for both first- and second-generation South Asians.
Firstly, negative circumstances leading to migration may contribute to later mental health
problems, for example traumatic events experienced by refugees of South Asian countries (Islam,
Khanlou, & Tamim, 2014). Next, post-migration issues such as the loss of social status and
support, separation from family, lack of employment, and difficulty integrating into Canadian
culture can contribute to poor mental health. Experiences of racism and discrimination may
further complicate matters and also negatively impact mental health (Samuel, 2009).
Furthermore, intergenerational conflict that may arise between first- and second-generation
Canadian South Asians has been reported as a risk factor for mental health problems including
stress, anxiety, depression, and identity loss (Islam, Khanlou, & Tamim, 2014; Samuel, 2009).
Mental Health Problems Among South Asian Women. While the issue of migration
may affect anyone in the community, research indicates clear gender differences in mental health

problems. In particular, Canadian South Asian women often report more mental health problems
than South Asian men due to stressors in social life, economic challenges, and navigating
between South Asian and Western cultures (Ahmed et al., 2005). Ahmed et al. (2005) conducted
focus groups with immigrant and newcomer South Asian women in the Greater Toronto Area and
described mental health problems which arose from a loss of social support, economic
uncertainty, downward social mobility, and a mechanistic lifestyle. A mechanistic lifestyle was
defined as busyness and lack of leisure time which led to women not completing expected daily
activities such as housework (Ahmed et al., 2005). Overall, the loss of social networks and
change in lifestyle negatively impacted the participant’s mental health (Ahmed et al., 2005).
Similar qualitative research conducted by Ekanayake, Ahmed, & McKenzie (2012) with South
Asian women experiencing depression in Toronto indicated that women explain their mental
health problems as a result of problems in their family or relationship, culture and migration, and
socioeconomics. Likewise, self-harm and suicide rates are greater among South Asian women
than men in Canada and the United Kingdom (Karasz et al., 2016). Younger women in particular
are at an increased risk of self-harm (Waheed & Husain, 2006). One literature review by Waheed,
& Husain (2006) found that South Asian women in the United Kingdom aged 16-24 were 1.5
times more likely to self-harm than White women.
Mental Health Problems Among South Asian Youth. Another area of concern is the
mental health of South Asian youth. Research regarding the mental health of South Asians have
typically focused on first generation, immigrant South Asian adults, however the limited research
on South Asian youth show that both first- and second-generation youth face unique challenges
which can lead to mental health problems. A meta-analysis by Sharma, Shaligram, & Yoon
(2020) identified challenges for second generation Canadian and American South Asian youth in

the family sphere, as well as within and outside the South Asian community contributing to poor
mental health.
Parent-child conflict is often cited as an area of concern for South Asian youth (Sharma,
Shaligram, & Yoon, 2020). As Sharma, Shaligram, & Yoon (2020) explain, expressions of
autonomy in sexuality, religious practices, and career choices during the adolescent stage in
development may be considered normal by Western standards; however, within the South Asian
context, they may also be perceived as disrespectful or disobedient to cultural values. Likewise,
differences in communication, rules, and values may further create stress within the family
(Sharma, Shaligram, & Yoon, 2020). Islam et al. (2017) identified similar areas of concern for
South Asian youth, in particular issues with ethnic identity, academic pressures, and family
difficulties have commonly been reported by participants. Issues with their ethnic identity arose
as parents and youth had to balance Western and South Asian cultures within one household
which often led to disagreement in navigating the two cultures. Additionally, pressures for
academic and career success often lead to stress in the household and lead to youth often
comparing their experiences in a strict household to their peers’ home environment.
Beyond the household, youth also experience acculturative stress when integrating to
both Western and South Asian cultures (Sharma, Shaligram, & Yoon, 2020). Here again we see
that women face increased burdens as the gender based cultural expectations to be modest, limit
dating or abstain from premarital sex conflict with Western expectations leading to increased
stress among South Asian women (Sharma, Shaligram, & Yoon, 2020). Similarly, a study by
Patel & Gaw (1996) found that immigrant South Asian young women had a higher risk of suicide
compared to South Asian men and older South Asian women in Canada. Likewise,
Canadian South Asian young women had a higher risk of suicide than young women in the

Indian subcontinent, reinforcing the idea that the conflict between South Asian and Canadian
expectations greatly contribute to mental health problems among South Asian women living in
Canada (Patel & Gaw, 1996).
Finally, both first and second-generation Canadian and American South Asian youth may
face a myriad of micro and macro-aggressions from outside of the South Asian community. For
example, harmful associations with terrorism because of one’s brown skin or wearing a turban or
hijab can contribute to mental health problems (Sharma, Shaligram, & Yoon, 2020). Perceived
discrimination is significantly correlated with psychological stress among both first-and
secondgeneration South Asians (Sharma, Shaligram, & Yoon, 2020). Similarly, Samuel &
Burney (2003) interviewed second generation South Asian university students in Ontario and
found all
22 of the participants had perceived experiences of racism from faculty and students on campus.
In particular, stereotypes such as the model minority myth created negative impacts on students’
well-being (Samuel & Burney, 2003).
Substance Use Among South Asians. Research on the experiences of substance use
among South Asian youth is limited, however there is a growing concern around the issue. A
recent review by Fraser Health Authority (2020) indicated that the number of overdoses has
increased by 255% among South Asians between 2015 and 2018 compared to an 138% increase
for non-South Asians in this region of Southern British Columbia. In contrast to research
highlighting greater prevalence of mental health problems among South Asian women, South
Asians who experienced overdose events were disproportionately young men. Stressors reported
by Canadian South Asian men included interpersonal conflict, suicidal ideation, and a history of

traumatic brain injury or motor vehicle accident (Fraser Health Authority, 2020). The report
highlights the need to address substance use and mental health problems within this community.
Other studies on the topic suggest that substance use is associated with 1) coping with
mental health problems and 2) integrating into Western culture. Research by Rastogi & Wadhwa
(2009) and Bhattacharya (1998) found that substance use among South Asian adolescents in the
United States is linked to coping with mental health problems including stress, depression, and
anxiety that arise from intergenerational conflict and destabilized family dynamics. Bhattacharya
(1998) further indicated that second generation South Asian American youth may use more
alcohol and drugs to help integrate into Western society, for example drinking or smoking at
parties. Finally, Islam et al. (2017) found that Canadian South Asian youth used substances to
cope with family problems and rebel against South Asian traditions. These findings suggest that
substance use among South Asian youth is linked to mental health problems which arise from
some of the issues previously mentioned, such as intergenerational conflict and integrating into
Western culture. Further investigation is needed to build on previous findings and consider how
the barriers to accessing mental health services may be related to substance use.
Mental Health & Substance Use During COVID-19
Impact on Mental Health. It is necessary to situate the issue of the increased prevalence
of mental health problems among members of the South Asian community in the context of the
current COVID-19 pandemic. Coronavirus disease (COVID-19) has disrupted the lives of
everyone as it bears consequences beyond physical health with impacts on personal and social
life, employment, school, and more. It is not surprising then that the pandemic has greatly
impacted the mental health of Canadians as many indicate that their mental health has worsened

since the start of the pandemic (Craig et al., 2022). The impact on mental health can be
associated with isolation, anxiety around the pandemic, and increased conflict at home (Craig et
al., 2022). A survey conducted with one thousand adults by the Centre of Addiction and Mental
Health (CAMH) (2021) revealed that one in five respondents reported moderate to severe anxiety
levels, feeling depressed, or feelings of loneliness during the pandemic. In comparison, in 2019,
the Canadian Community Health Survey found approximately 14% of Canadians aged 12 or
older reported a mood or anxiety disorder suggesting an increase in mental health problems
among Canadians (Statistics Canada, 2020). Additionally, gender differences have been exhibited
such that 24% of women report feelings of loneliness compared to 18% of men (CAMH, 2021).
Findlay, Arim, & Kohen (2020) and Miconi et al. (2021) report similarly; those most at risk of
reporting poor mental health due to the pandemic include women and youth, even after
considering socioeconomic and health factors.
Narrowing in on the South Asian diaspora, one survey indicates that this community is
especially at risk of poor mental health during and post-pandemic (Moyser, 2020). Moyser
(2020) found that among other visible minorities, Canadian South Asians reported the highest
prevalence of self-rated poor mental health and increased anxiety since the start of the pandemic.
One reason for the negative impact on mental health may be the increased exposure associated
with COVID-19. Miconi et al. (2021) conducted an online survey measuring mental health
outcomes as well as COVID-19 discrimination and stigma in Quebec. The authors found that, of
the 3231 participants, Black (38.7%), Arab (33.5%), and South Asian (28.7%) participants
reported higher exposure to the virus compared to White and Asian participants (Miconi et al.,
2021). Higher exposure to the virus may be the result of overrepresentation of Canadian South

Asians in low wage, essential work such as grocery stores, public transportation, and factories
(Thobani & Butt, 2022). These work environments may not be able to adequately implement
public health measures such as social distancing and thus, those working in these frontline jobs
are at an increased risk of contracting the virus (Thobani & Butt, 2022). Similarly, South Asians
are at a greater risk of becoming seriously ill from the virus as pre-existing conditions such as
cardiovascular disease and diabetes are more common among South Asians compared to White
Canadians (Thobani & Butt, 2022).
Exposure to COVID-19 may also be associated with increased discrimination as Miconi
et al. (2021) found that East and South Asians in Canada reported the highest prevalence of
experiencing COVID-19 discrimination (31.4% and 30.1% respectively), that is the perceived
discrimination experienced for COVID-19 status (Miconi et al., 2021). Similarly, Jaspal & Lopes
(2021) conducted a survey with 226 Black and South Asian participants in the United Kingdom
and found that South Asian participants reported significantly more religious discrimination than
Black participants, presumably due to growing Islamophobia. The authors found that
discrimination was directly associated with fear of contracting COVID-19 which in turn was
associated with a decreased life satisfaction, increased depression and generalized anxiety (Jaspal
& Lopes, 2021). Overall, both exposure to the virus and associated discrimination contributed to
poorer mental health (Miconi et al., 2021).
Impact on Substance Use. Worsening mental health as a consequence of the pandemic
may also lead to increased substance use, especially for individuals with pre-existing mental
health problems (Vigo et al., 2020). A survey by Rotermann (2020) found that substance use was
higher among Canadians who reported lower mental health status since the beginning of the
pandemic compared to those who did not report lower mental health. In addition to the mental

health findings, CAMH (2021) also revealed that 26% of respondents report binge drinking in
the previous week, with men significantly more likely to report binge drinking compared to
women though the authors do not indicate how many of those who reported binge drinking also
reported worsening mental health. MacMilan et al. (2021) conducted an online survey with 1405
participants across Canada and the United States measuring concerns around the pandemic and
alcohol and substance use and found that one third of participants reported using alcohol or
substances to cope during the pandemic. In particular, higher alcohol and substance use was
associated with those more personally affected by COVID-19 (e.g., contracting the virus or
knowing someone else who contracted the virus), more likely to experience childcare challenges
during the pandemic, and less associated with a religious community (MacMillan et al., 2021).
Another study by Craig et al. (2022) examined youth (12-18 years old) mental health and
substance use during the pandemic through an online survey with 809 participants across
Canada. In addition to finding that women and trans and non-binary youth experience more
pandemic related stress compared to men, the authors found that over 50% of youth used
substances in the last three months and about 20% reported regularly using substances at least
once a week. However, without information on substance use prior to the pandemic, it is unclear
if current consumption is associated with the pandemic or poor mental health. Nonetheless, it is
clear that the pandemic is causing great strains on the mental health of Canadian South Asians
and moreover, some links have begun to emerge between poor mental health and increased
alcohol and substance use especially among youth, however there is currently a gap in our
understandings of how South Asian youth specifically are coping with the pandemic.

The Underutilization of Mental Health Services Among the South Asian Diaspora
Despite the prevalence of mental health problems among the South Asian community in
Canada, research shows that South Asians underutilize mental health services. A study by Tiwari
& Wang (2006) found that compared to White participants, immigrant Asians who received a
diagnosis of major depressive disorder were less likely to use mental health services in Canada.
Likewise, a study by Chui et al. (2018) reported that compared to White participants, Asian
participants living in Canada were less likely to seek out mental health support and consequently,
had lower rates of mental health diagnoses. Similarly, Li & Browne (2000) conducted interviews
with 60 Asian Canadian adults about their mental health and barriers to accessing mental health
services and found that participants often perceived mental health problems as serious and
untreatable (Li & Browne, 2000). Additionally, the authors found that immigrant Asians report
language barriers (i.e., lack of proficiency in English) and health practitioners discounting Asian
culture as the two most common types of barriers impeding mental health service use (Li &
Browne, 2000).
Looking at the experiences of racialized communities in the United Kingdom, where they
may have similar experiences to racialized communities in Canada navigating in a Euro-centric
mental health service system, a qualitative study by Memon et al. (2016) indicated two major
themes that affected access to mental health services among Black and Asian communities in
Southeast England. Firstly, personal and environmental factors such as public stigma, reluctance
to speak about psychological distress among men, cultural identity, and financial factors
commonly affected help seeking behaviour (Memon et al., 2016). Second, the relationship
between the service user and mental health service provider, which may be affected by long

waitlists, language barriers, power imbalances, and inadequate recognition of mental health
needs also affected participants’ ability to access mental health services (Memon et al., 2016).
Looking more closely at the relationship between service providers and service users,
waitlists result in leaving mental health problems unaddressed and at times, leads to a worsening
of mental health problems (Memon et al., 2016). On the other hand, language barriers and
communication problems reflect the service user’s inability to adequately express mental health
problems and service provider’s failure to listen to the concerns and needs of the service user
respectively. Likewise, participants state that healthcare providers did not adequately respond to
service user’s needs and express the lack of flexibility to supporting people’s preferences
including individual or cultural preferences (Memon et al., 2016). For example, participants
discussed the overemphasis of medication to treat mental health problems and feeling
discouraged to explore other therapy modalities that would have allowed them to discuss their
concerns more creatively (Memon et al., 2016). Participants also discussed a general feeling of
powerlessness as mental health service users (Memon et al., 2016). Participants felt that service
providers often talked down to them and did not allow for input from service users creating a
sense of helplessness and passivity (Memon et al., 2016). Lastly, participants report cultural
insensitivity and discrimination from White service providers including an inability to discuss
issues of racism and receiving different types of treatment compared to White counterparts
(Memon et al., 2016). For example, one participant explained that they did not receive a referral
to a specialist from their general practitioner while their White friend who expressed similar
mental health concerns did (Memon et al., 2016).
The majority of the existing literature on the issue of service utilization focuses on the
Asian community as a whole and given the heterogeneity of this population, the studies do not

provide in-depth information on the experiences of South Asians especially South Asian youth as
current research typically focuses on adults. Research on the specific experiences of South
Asians accessing mental health services is far more limited. The following studies examine the
experiences of South Asians accessing mental health services. The findings highlight several
problems with mental health services that create barriers to effective treatment for South Asians.
A content analysis conducted by Inman et al. (2014) on the psychological research
conducted in the last three decades with the South Asian community in the United States found
that South Asian Americans identified experiences with racial discrimination, internalized
stereotypes, and health professionals’ lack of cultural knowledge as the primary barriers they
faced when accessing mental health services. Islam et al. (2017) conducted semi-structured
interviews with South Asian youth in the Peel Region. Interviews covered various topics
including mental health stressors and barriers to accessing mental health services. Regarding
barriers to mental health services, participants noted mental health stigma, lack of South Asian
representation among mental health professionals, fees for services not covered by the Ontario
Health Insurance Plan (OHIP), long wait times, and a lack of specialization on youth issues as
primary barriers (Islam et al., 2017). Furthermore, youth noted that conceptions of mental health
treatment were highly westernized and overemphasized medication (Islam et al., 2017).
A literature review of 15 studies conducted by Prajapati & Liebling (2022) investigated
the experiences of adult South Asian mental health service users in the United Kingdom and
found three themes in line with other existing literature. Firstly, service users were “distanced”
from services (Prajapati & Liebling, 2022). This distance was due to services being outside
participants’ awareness or outside participants’ cultural norms and practices which discouraged
help seeking behaviour such as cultural stigma and difficulties disclosing private information

(Prajapati & Liebling, 2022). Second, participants described difficulties trusting service
providers (Prajapati & Liebling, 2022). Participants reported being wary of trusting White mental
health professionals as they lacked cultural awareness and did not acknowledge the complexities
of their mental health problems (Prajapati & Liebling, 2022). On the other hand, issues such as
stigma and confidentiality made it difficult for participants to trust South Asian mental health
professionals (Prajapati & Liebling, 2022). Thirdly, the participants described services as a threat
to their cultural identity referring to a lack of cultural sensitivity and collaborative care between
the service provider and user (Prajapati & Liebling, 2022).
A study by Bowl (2007) provides another perspective to understand the issue of mental
health service utilization among the South Asian community. Conducting focus groups with
South Asian mental health service users in the United Kingdom, the author highlights three
dimensions of exclusion that contribute to barriers to accessing effective mental health support:
cultural, institutional, and socioeconomic exclusion (Bowl, 2007). Cultural exclusion refers to
the inability of mental health service providers to understand service users who are not from
White populations (Bowl, 2007). This goes beyond a lack of understanding due to language
barriers and includes difficulties in understanding what service users want and issues with
standard psychiatric assessments (Bowl, 2007). Participants who were in-patients at hospitals
discussed service providers not taking into account cultural practices, for example not providing
space for prayer (Bowl, 2007). Institutional exclusion refers to mental health services not
acknowledging racial and cultural differences of service users which may contribute to poor
mental health, for example a lack of focus on how family and community related issues impact
mental health (Bowl, 2007). Finally, socioeconomic exclusion refers to how lower
socioeconomic status and stressors associated with it can contribute to poor mental health. For

example, employment and financial issues were reported as stressors that contributed to poor
mental health for South Asian men (Bowl, 2007). These issues were exacerbated by race as
language barriers and racism can further affect socioeconomic status (Bowl, 2007). These
dimensions of exclusion speak to difficulties South Asians in the United Kingdom have in
participating in standard mental health services which do not integrate an understanding of
cultural and social factors that contribute to poor mental health (Bowl, 2007).
The current literature points to a number of reasons why South Asians across Canada, the
United States, and United Kingdom are experiencing barriers to effective mental health services.
To explore these barriers further and understand why they arise, we can organize them into three
(inter-related) major factors: mental health stigma, poor provider-client experiences, and systems
level issues with mental health services. Exploring these factors will shed light on how they
result in low service utilization among Canadian South Asians.
Mental Health Stigma. A critical barrier to receiving mental health support cited in the
mentioned research is mental health stigma. Gary (2005) defines mental health stigma as the
“collection of negative attitudes, beliefs, thoughts, and behaviours that influences [an] individual,
or the general public, to fear, reject, avoid, be prejudiced and discriminate against people with
mental disorders.” (p. 980) Stigma manifests in many ways, including verbally through language
and physically through behaviour (Gary, 2005). Two common forms of mental health stigma that
are often studied are public/perceived stigma and personal/self-stigma. Public stigma refers to
the discrimination towards individuals with mental health problems because they are perceived
as socially unacceptable (Arora, Metz, & Carlson, 2016). On the other hand, personal stigma
refers to an individual’s own stigmatizing views (Arora, Metz, & Carlson, 2016). Personal stigma
is associated with lower self-esteem and self-efficacy and creates a sense of helplessness

regarding accessing mental health support (Gary, 2005). Related to the concept of stigma is
prejudice and discrimination which reflect stereotypes of minority groups including racialized
groups and individuals with mental health problems (Gary, 2005). Both prejudice and
discrimination can perpetuate and deepen personal and public stigma experienced by those
experiencing mental health problems.
Stigma is often discussed in the field of mental health because it can be a barrier to
accessing mental health services. While public stigma is often thought to be linked to low mental
health service use, research has found that, for members of the South Asian community, personal
stigma is negatively associated with help seeking attitudes (Loya, Reddy, & Hinsaw, 2010).
Studies by Loya, Reddy, & Hinsaw (2010) and Arora, Metz, & Carlson (2016) found that South
Asian American college students with poor attitudes towards mental health services also showed
increased levels of personal stigma compared to those with better attitudes about mental health.
Increased personal stigma may be the result of traditional cultural values for some South Asian
students, including social conformity, emotional restraint, and discomfort with self-disclosure
(Arora, Metz, & Carlson, 2016). These values may encourage individuals to conceal their mental
health problems and deter help seeking behaviour. Moreover, Arora, Metz, & Carlson (2016)
found gender differences in stigma such that South Asian American women were more willing to
seek mental health services than men. This likely reflects gender expectations for men to be
strong and in control (Arora, Metz, & Carlson, 2016). Thus, personal stigma towards mental
illness can act as a strong barrier to accessing mental health services among this population.
Poor Service Provider-Client Relationships. Beyond personal stigma, South Asians
may also be stigmatized or discriminated against by healthcare providers which may further
prevent help seeking behaviour. Gary (2005) suggests that Black, Indigenous, and People of

Colour (BIPOC) experiencing mental health problems face double stigma as they are both part of
a minority group and experience mental health problems. The term “double stigma” refers to how
“minority group members with mental illnesses endure discriminatory practices from numerous
segments of society, including politicians, researchers, and clinicians” (Gary, 2005, p.
981). Racialized minorities with mental health problems show significantly lower levels of
access to mental health services and poorer mental health outcomes when compared to White
counterparts (Gary, 2005). In this case, a lack of cultural competency, racist stereotypes and
discrimination interact and promote power imbalances between the service provider and client
which may deter help seeking behaviour. South Asians may be more likely to be discriminated
against, mistreated, and misdiagnosed by mental health providers and as a result, build distrust
towards the mental health system which ultimately leads to underutilization of services (Gary,
2005).
Incompatible Mental Health Services. A final piece regarding low mental health service
utilization within the South Asian community revolves around the differences in conceptions of
mental health treatment. The dominant forms of mental health services in Canada reflect a
biomedical and individualized conception of mental illness (Ekanyake, Ahmed, & McKenzie,
2012). For example, mental illness may be seen as a result of genetics or irregular neurochemical
production in the brain (Ekanyake, Ahmed, & McKenzie, 2012). This contrasts with South Asian
conceptions of mental illness which are largely situational and social in nature (Ekanyake,
Ahmed, & McKenzie, 2012). For example, South Asian women in Canada report their depressive
symptoms to result from problems with family and relationships, culture and migration, and
socioeconomics (Ekanyake, Ahmed, & McKenzie, 2012). Differences in the conceptions of
mental illness may lead to different ideas of what treatment and healing look like. This is

highlighted by the success of the modified mental health programs developed by Karasz et al.
(2015) and Naeem et al. (2015). These programs are modified mental health services that better
suit different populations of South Asian women.
Karasz et al. (2015) started the Action to Improve Self-Esteem and Health (ASHA)
project, a mental health intervention targeting Bengali Immigrant women with depression in the
Bronx. This project was based on participants’ conceptions of distress that focused heavily on
social isolation and financial dependence and thus, in addition to providing mental health
treatment, the program helped increase asset building (Karasz et al., 2015). Asset building
involved matched savings accounts funded by the U.S. Department of Health and Human
Services where women deposited $10 a week in addition to receiving financial literacy training.
Participants showed a reduction in depressive symptoms and saved an average of $10 per week
which was put towards starting a small business and enrolling in community college (Karasz et
al., 2015).
Similarly, Naeem et al. (2015) adjusted a cognitive behavioral therapy (CBT) program for
South Asian Muslims in the United Kingdom. This program was modified to better suit
collectivists cultures by increasing awareness of culture and religion, creating different forms of
assessment, reducing barriers between the service providers and clients, and adjusting therapy
technique tools to improve accessibility (Naeem et al., 2015). These projects highlight the
potential for improved mental health services for South Asians, however they are far from
commonly employed within the mental health field. Moreover, the Naeem et al. (2015) and
Karasz et al. (2015) studies are targeted towards South Asian adults, thus more work is needed to
adjust mental health services for different South Asian groups including youth. Regardless, these
two studies demonstrate that mental health services as they currently are delivered are

insufficient in improving the mental health of South Asians, hence leading to underutilization of
these services.
The current research on mental health service utilization among Canadian South Asians
cannot be understood as simply identifying a failure on the part of the individual to seek out help
for their mental health. There are many problems with the mental healthcare system that create
barriers for individuals to access services. However, more research is needed on the experiences
of South Asian youth and how stigma, provider-client experiences, and different kinds of mental
health support affect their experiences with accessing services.
Research Gaps
Based on the background research provided, there are several gaps in the literature. First,
qualitative research on the experiences and barriers to accessing mental health services is limited.
Current research heavily focuses on quantitative data, such as surveys. As a result, qualitative
research that provides participants with the space to express their experiences with mental health
services is lacking and is much-needed.
Next, the majority of research regarding mental health among the South Asian community
typically focuses on immigrant adults with less investigation on youth (Inman et al., 2014). In
particular, youth who are second generation South Asian-Canadians may experience racialization
differently than immigrant counterparts. For example, Sundar (2008) describes how second
generation South Asian youth are flexible in their identity as a South Asian and Canadian and
will bring aspects of either identity to the forefront when advantageous. This malleable nature of
their identity can lead to youth being racialized as more “Canadian” than South Asian immigrants
and newcomers. Likewise, attitudes towards mental health services may differ between first

generation South Asians adults and second generation South Asian youth as research show that
youth are more willing to discuss their mental health problems whereas youth describe their
parents as more likely to exhibit stigma and conceal mental health problems from the community
(Islam et al., 2017).
Relatedly, issues of substance use, which are often related to mental health problems, may
be particularly relevant for youth, as existing studies suggest that substance use is one way to
cope with mental health problems (Rastogi & Wadhwa, 2009; Bhattacharya, 1998). More indepth
research on the experiences of South Asian youth using substances is required to identify how
youth perceive their own substance use and how the pandemic may have impacted consumption.
Asian Critical Theory & Mental Health Services
Understanding the underutilization of mental health services among members of this
community involves looking beyond individual reasons and investigating the larger structures
that affect the experiences of being South Asian in Canada. To bridge the previous background
research to these structures, I will be using the Asian Critical Theory (AsianCrit) by Iftikar &
Museus (2014). AsianCrit is a branch of Critical Race Theory (CRT), a theory originally
developed in the field of legal scholarship. Under this theory, the inequities of society are
understood to be a result of racial hierarchies and the normalization of racism (Riemer et al.,
2020). The AsianCrit theory utilizes these core principles of CRT to understand issues specific to
the Asian community. Western society often racializes Asians into a single group resulting in
similar experiences of oppression, thus despite the heterogeneity of this community, the
AsianCrit theory is suitable for all Asians, including the South Asian community. Iftikar &
Museus (2018) describe seven tenets of AsianCrit which can be used to understand how White
supremacy shapes the experiences of Asians: asianization; transnational context; (re)constructive

history; strategic (anti)essentialism; intersectionality; story, theory, and praxis; and commitment
to social justice. These seven tenets can also be used to guide community mental health research
as well as understand barriers to accessing mental health services.
Asianization. Asianization refers to the racialization process of Asians in North America
and the way in which White supremacy is intrinsically woven into this process (Iftikar &
Museus, 2018). In particular, Asians are often racialized as foreigners, model or deviant
minorities, or sexual deviants (Iftikar & Museus, 2018). The model minority myth refers to the
ways in which Asians are expected to succeed in work and school settings in North American
(Iftikar & Museus, 2014). This racialization process ensures that Asians are always perceived as
the “other” in North America. This in turn informs laws, policies, and programs that
systematically exclude Asians, such as the Chinese Immigration Act in 1923 (Iftikar & Museus,
2018).
To develop the asianization tenet further, we need to understand what Harpalani (2013)
coins as racial ambiguity. Harpalani’s (2013) DesiCrit is a branch of CRT tailored towards the
South Asian community. While it was developed in the area of legal scholarship, the theory’s
emphasis on the concept of racial ambiguity is relevant to understanding the specific racialization
process of South Asians in North America. Harpalani (2013) describes racial ambiguity as “the
changing racial characterization of a person or group, depending on the local and historical
context.” (p. 83). When South Asians began to arrive in Canada, their place in the country’s
racial hierarchy was uncertain (Ghosh, 2017). Unlike Black, White, or Indigenous peoples, South
Asians arrived in Canada fairly recently and moved around the racial hierarchy throughout
history where their status in Canada shifted from being equal to or inferior to White people at
different time points (Ghosh, 2017).

Moreover, the diverse physical features and cultural and religious practices among
members of the South Asian community further contribute to racial ambiguity; for example,
Christian South Asians may be privileged in ways that Muslim South Asians are not (Harpalani,
2013). Consequently, South Asians are racialized in diverse ways against different racial groups.
For example, in comparison to White people, South Asians may be perceived as foreigners, thus
upholding ideas of White supremacy. On the other hand, in comparison to Black people, South
Asians may be racialized as model minorities who have successfully integrated into Western
society and act as a model for other minority groups, suggesting that Asians are better or more
successful than the Black community and perpetuating anti-Blackness in Canada. In summary, this
racialization process is fluid and changes depending on the context.
These varying forms of racialization can contribute to both the development of mental
health problems and the underutilization of mental health services. Problems that arise from
navigating between Western and South Asian cultures can be understood as a product of South
Asians being racialized as the “other”. By constantly being perceived as a foreigner or excluded
from dominant racial groups, South Asians may feel that they need to conceal their South Asian
heritage in order to integrate into Western society (Sundar, 2008). Attempts to conceal South
Asian heritage may cause distress for both the individual and their family leading to
intergenerational conflict (Sundar, 2008). Likewise, being perceived as a foreigner may affect the
extent to which South Asians are willing to access mental health services as they may feel that
these services are not compatible for members of their community (Inman et al., 2014; Karasz et
al., 2016). Similarly, the model minority stereotype promotes personal stigma of mental illness as
it reinforces the minimization or concealment of mental health concerns as the stereotype
suggests that Asians are always successful (Inman et al., 2014).

Transnational Context. Transnational context refers to the importance of situating the
experiences of Asians and the effects of White supremacy within both individual and larger
networks of global economic, political, and social processes (Iftikar & Museus, 2018).
Understanding both the past and present global processes shape conditions for Asians in Canada,
including experiences of racism (Iftikar & Museus, 2018). Consequently, these processes can
have a negative impact on the mental health of Asians in Canada. For example, the current
COVID-19 pandemic has fueled anti-Asian racism around the world which may in turn affect the
mental health of Asians living in Canada as well as their ability to access services for their
mental health (Misra & PhuongThao, 2020)
(Re)constructive History. (Re)constructive history refers to how Asians are typically
invisible in North American history and speaks to the need to break this silence and create a
collective Asian historical narrative (Iftikar & Museus, 2018). As already stated, the history of
South Asians in Canada is a short one as the majority of South Asians arrived in Canada within
the last 80 years. In the context of the current study, attention needs to be paid to how recent
events can contribute to mental health problems and barriers to accessing mental health services
for South Asians. For example, the increase in Islamophobia following 9/11 and Muslim Ban in
2017 in the United States are events in recent history that have negatively impacted the wellbeing
of South Asian Muslims and even South Asians who are not Muslim but are none the less
perceived as such (Smari, Alcala, & Sharif, 2018).
Strategic (Anti)essentialism. Strategic (anti)essentialism refutes ideas of essentialism
that understand social identities independently of each other. In other words, essentialist
philosophy asserts that there is an essence to an experience (Grillo, 1995). For example, under

essentialism, there is an essential experience for all women regardless of other identities, such as
race or sexual orientation. Similarly, the ways in which South Asians may be racialized as
foreigners and model minorities essentialize their identity and experiences. Strategic
antiessentialism opposes such ways of thinking and instead, understands the experiences of
Asians as an integrated identity. In the context of mental health, Western society’s proclivity to
view mental health experiences as a matter of biological processes suggest that mental illness has
an essential experience, thus aligning with ideas of essentialism. In reality, the social world can
vastly influence mental health experiences. Socioeconomic status, racism, stigma, and
discrimination can affect mental health experiences, especially for South Asians who have
overwhelmingly stated social factors as contributors for mental health problems (Karasz et al.,
2016). This discrepancy in how the West views mental illness and diverse ways in which South
Asians experience mental health problems can result in dominant mental health treatments to be
ineffective for South Asians, thus reducing the willingness of members of this community to seek
out care.
Intersectionality. Intersectionality in AsianCrit theory refers to how White supremacy
and other systems of oppression intersect, exploit, and shape the experiences of Asians (Iftikar &
Museus, 2018). Taking an intersectional lens on this issue highlights how South Asian women
are not only more likely to experience mental health problems as already mentioned but reveal
the increased need for culturally appropriate mental health support for South Asians. Cultural
expectations and traditions put an increased burden on South Asian women thus, mental health
services need to be tailored to address such issues. Likewise, other intersections that may not be
explored extensively in the current study but remain important to note include disability, sexual

orientation, and religious affiliations that may increase vulnerability to mental health problems
and require further specialized care.
Story, Theory, and Praxis and a Commitment to Social Justice. The final two tenets:
story, theory, and praxis and commitment to social justice speak to the research process by
ensuring that the research undertaken creates meaningful change in the community. Story, theory,
and praxis refers to how the experiential knowledge of Asians can challenge the dominant
narratives constructed by White supremacy and shift focus on the realities of Asians (Iftikar &
Museus, 2018). Finally, a commitment to social justice refers to how the utilization of this theory
is part of a larger process to ultimately end forms of oppression and exploitation (Iftikar &
Museus, 2018). These tenets are foundational to Community Psychology research and guide the
entire research project. The barriers South Asians face when accessing mental health services can
result in mental health problems being unaddressed and ultimately creating a greater burden.
Identifying these barriers is the first step in finding solutions to improve access to services to
improving the wellbeing of members of this community.
Theoretical Framework: An Adapted AsianCrit Framework for Mental Health Service
Utilization
To better understand Canadian South Asians experiencing mental health problems and
any experiences they have with mental health services, this study is using an adapted AsianCrit
framework (Figure 1) that utilizes the relevant tenets of the theory and brings together other
important concepts of mental health based on background literature.
Figure 1
An Adapted AsianCrit Framework for Mental Health Service Utilization
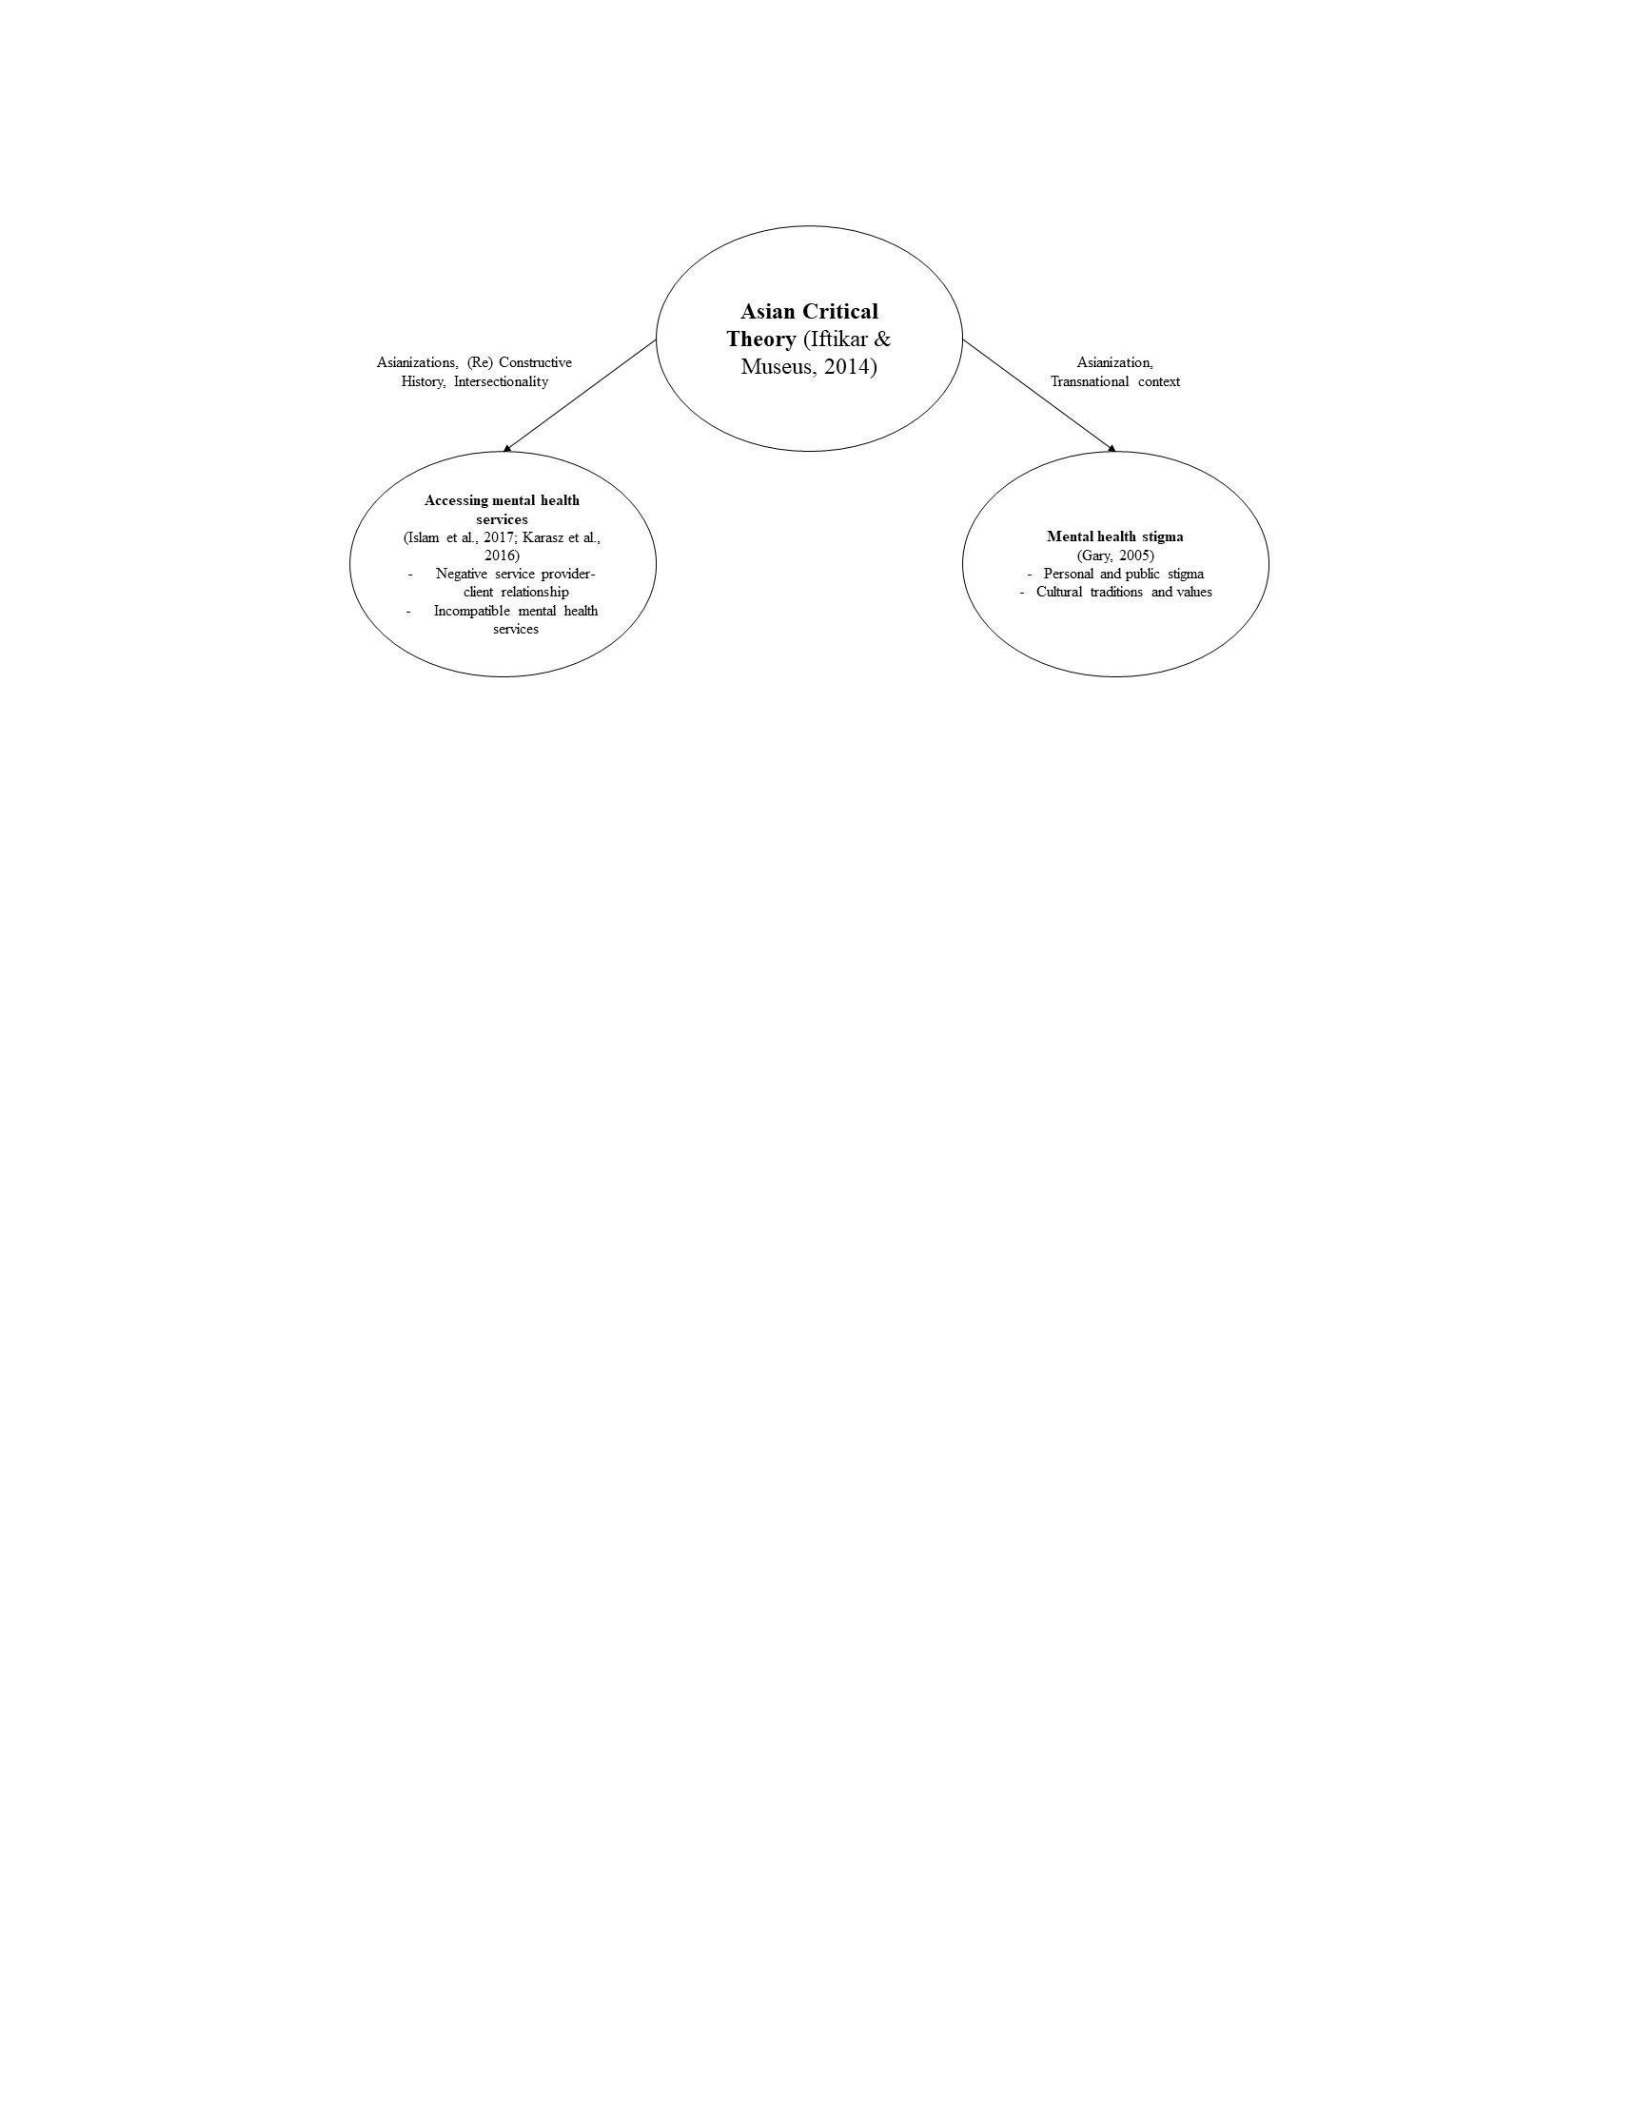
The underutilization of mental health services among the South Asian community can be
understood as a result of two overarching factors: 1) problems with the mental health system
which include poor service provider-client relationships and incompatible mental health services
and 2) mental health stigma. Firstly, Canada’s mental health system currently does not meet the
needs of the South Asian community. As mentioned earlier, issues with the mental health system
arise from poor provider-client experiences and ineffective services. This aspect of the model can
be tied to the AsianCrit tenets, asianization, intersectionality, and (re)constructive history.
Understanding the ways in which South Asians are racialized into Canadian society
illustrates not only why mental health problems may occur, but also why South Asians may be
receiving inadequate mental health services. Being racialized as a foreigner in Canada because of
the ways in which White supremacy dominates North American society can lead to
discriminatory behaviour from service providers who are not South Asian. Stereotypes,
unconscious biases, and a lack of cultural awareness stemming from the racialization process can
result in misdiagnoses, limited access to treatment, and poor communication, ultimately leading
to health inequities (Arora, Metz, & Carlson, 2016). Likewise, mental health services are not

being developed with the needs of South Asians in mind, but rather they reflect Western
understandings of mental illness (Islam et al., 2017). This in turn may lead South Asians to find
mental health services incompatible with their own values. Further, an intersectional lens is
important as South Asians can experience further marginalization due to intersections with
gender and sexuality, for example. These intersections can create unique experiences in the ways
in which South Asians are accessing mental health services. Finally, there is a need to reconstruct
the current narratives of South Asians, particularly to dispel the model minority myth and engage
more in-depth with South Asians on their experiences accessing mental health services.
Another key reason why South Asians may not seek out mental health services is mental
health stigma. As mentioned earlier, stigma may be fueled by cultural values and complicated
with its intersection to race and ethnicity as South Asians experiencing mental health problems
likely experience double stigma which ultimately affect mental health outcomes (Gary, 2005).
This aspect of the framework connects to the AsianCrit tenets, asianization and transnational
context. Regarding the asianization tenet, the model minority myth may promote the
concealment of mental health symptoms and increase stigma experienced by South Asians
ultimately leading to reduced service utilization (Inman et al., 2014). Regarding the transnational
context tenet, stigma and related cultural factors that create barriers to accessing services must be
understood within larger social processes. For example, increases in Islamophobia, and Asian
hate during the COVID-19 pandemic can further stigmatize South Asians experiencing mental
health problems (Lee & Jang, 2021). Understanding this context can also inform useful
interventions to reduce stigma and promote mental health services that align better with South
Asian experiences and values.

Research Objectives
The above literature review suggests that South Asian youth experience cultural barriers
such as stigma that prevent help seeking behaviour. Additionally, South Asian youth have unique
mental health needs and experiences navigating White supremacy that often lead to negative
experiences accessing mental health services (Islam et al., 2017; Inman et al., 2014; Rastogi &
Wadhwa, 2009). Using the AsianCrit Theory, the present study attempts to understand and
explore these experiences in depth especially in the context of the COVID-19 pandemic in order
to identify how to improve access to mental health services for South Asian youth moving
forward.
Research Questions
In order to address the gaps mentioned, this project seeks to answer the following
questions: what are the experiences of South Asian youth with mental health problems of
accessing mental health services in the Greater Toronto Area (GTA)? What are facilitators or
barriers that have affected how South Asian youth are accessing mental health services?
Additional secondary questions include: How do present mental health problems and the barriers
to accessing mental health services contribute to substance use for South Asian youth?; and, How
has COVID-19 changed how South Asians are accessing mental health services?
Significance of Research
The current project will increase knowledge in the field of community mental health
research. Faulkner’s (2017) examination of the power of experiential knowledge highlights the
significance this project can have for the community of South Asian youth living in Canada.

Understanding their experiences of mental health problems and how they navigate mental health
services can serve as a way to critique the current mental health system and empower members of
the community by giving them a voice in a conversation from which they have often times been
excluded. Moreover, this experiential knowledge is situated in other knowledge surrounding
discrimination and stigma both in the context of mental health and race. This research can further
knowledge in the field of community mental health by continuing to address the mental health
concerns of marginalized communities and decentering White voices in conversations of mental
health.
Further, this project is especially important right now as the COVID-19 pandemic
continues to affect the mental health of the entire population. As noted, South Asians are
reporting lower mental health and increased anxiety as a result of the pandemic (Moyser, 2020).
Failure to recognize and address the unique barriers faced by members of the South Asian
community will result in mental health problems that remain unsupported and further
marginalize members who may already face racial and gender-based oppression. By bringing
South Asian voices to the forefront, further work can be done to address the barriers South
Asians experience when accessing adequate mental health services whether it is to tailor mental
health services to better meet the needs of this community or create strategies to reduce mental
health stigma.
Methods
Research Paradigm
This research project is guided by a constructivist paradigm. Constructivism denies the
idea of objectivity and instead, it is founded on the assumption that reality is constructed by the

observer (Allen, 1994). What is considered fact, under this paradigm, is the result of the values,
meanings, and attitudes of both the researcher and participant (Allen, 1994). Thus,
constructivism situates participant responses in their cultural, societal, and historical context
(Allen, 1994). A constructivist paradigm aligns well with the current theoretical framework as
constructivism, like the AsianCrit theory, emphasizes the context in which participants are
sharing their experiences. For the present study, situating participant’s experiences within
systems of oppression such as racism, discrimination, and stigma, as identified through the
theoretical framework, can demonstrate how the issue of service utilization is systemic in nature
rather than the result of individual decisions.
The use of a constructivist paradigm also encourages participants to make meaning of
their experiences with the researcher during the interview process and during member check in.
For example, participants have the space to reflect on their experiences with mental health
service utilization and consider why they may have had certain positive or negative experiences.
This reflective process is essential to the study as there is no objective experience for mental
health service utilization. Instead, we can only gauge at how South Asian youth feel about their
experiences and let that guide future research and action. Similarly, as a researcher, my own
worldview, including my experiences as a South Asian women and Community Psychology
masters student, shape how I understand the experiences shared by participants and formulate the
findings for this project.
Research Design
The current research questions and objectives are appropriately addressed with
semistructured interviews. As mentioned, one of the objectives of the research explores the

experiences around mental health and mental health services. As these experiences are nuanced,
they require open ended questions and flexibility to explore a number of different topics related
to mental health as well as how participants’ mental health, culture, socioeconomic status, and
social networks and identities such as gender, sexuality, or even age shape their experiences
accessing mental health services (Wilig, 2008).
Further, as indicated in the literature review, research on the utilization of mental health
services among members of the South Asian community have thus far relied heavily on
quantitative measures (see, e.g., Tiwari & Wang, 2008; Karasz et al., 2016; Chui et al., 2018).
These studies do not adequately describe the barriers South Asians face when accessing services.
The existing qualitative studies tend to focus broadly on South Asian mental health including the
factors contributing to mental health problems. In general, there is limited emphasis on the
experience of service utilization and how the barriers South Asians experience relate to systemic
problems. The current study places a greater emphasis on the issue of service utilization by
investigating the experiences of both individuals who have sought out mental health services and
those who experience mental health problems but have not sought out mental health services and
further, connecting these experiences in the context of the COVID-19 pandemic. Thus, there is a
clear gap in qualitative research for this topic and while some studies have begun to fill this gap,
there is more work needed to fully address the problem.
Participants
Participant recruitment. I employed a number of recruitment strategies. I collaborated
with Access Alliance to aid in participant recruitment and knowledge dissemination. Access
Alliance is a multicultural community organization that focuses on improving the health

outcomes of Torontonians (Access Alliance, n.d.). This organization works with various partners
to address health inequalities with those most vulnerable including refugees and immigrant
communities (Access Alliance, n.d.). In collaborating with this organization, Access Alliance
shared the study poster (Appendix A) internally with other researchers who shared the posters
within their own networks. Due to the province wide lockdown that occurred during the study
recruitment period, Access Alliance was unable to promote the study in person within their
building as originally planned. This overall limited the extent to which Access Alliance was able
to assist in participant recruitment.
In addition to connecting with Access Alliance, a number of South Asian university clubs
were contacted over email requesting club leaders to forward an email advertising the study to
their club members. Some of the clubs that were contacted include South Asian Alliance
(including members from Toronto Metropolitan University, York University, and University of
Toronto), Bangladeshi Student Association (University of Toronto), Indian Alumni Association
(University of Toronto), and Muslim Student’s Association (University of Toronto).
Finally, what proved to be the most successful strategy for participant recruitment was the
advertisement of the study through Instagram. An Instagram account (@samentalhealthproj) was
created to promote the study. Several members of the South Asian community and Toronto based
organizations or networks that focus on mental health and serving youth and/or racialized
communities were contacted to share the recruitment poster through Instagram. The recruitment
poster was shared with over 20 Instagram accounts.
Sampling. This study used purposive sampling as the research project was looking for
South Asian youth who are experiencing mental health problems. In particular, maximum

variation and snowball sampling was used. Maximum variation sampling aims to capture a
heterogeneous sample, so that participants varied in terms of age, gender, whether or not they
grew up in Canada, and whether or not they have accessed mental health services (Paggett,
2012). In order to achieve maximum variation, the recruitment poster was shared in different
spaces that would allow for information on the study to reach a diverse number of South Asian
youth. For example, sharing the recruitment poster with Access Alliance and Instagram accounts
of other mental health organizations increased chances of recruiting participants who already
sought out mental health services. Similarly, reaching out to organizations that support queer
South Asians allowed for the perspectives of queer South Asian youth experiencing mental health
problems. Next, snowball sampling, which involves reaching out to participants to recruit others
in the target population, was used as many participants described knowing other South
Asian youth who had shared similar experiences regarding accessing mental health services
(Paggett, 2012). In a follow-up email thanking participants for taking part in the study,
participants were also encouraged to share this project within their networks.
Sample size. Based on Hennink & Kaiser’s (2021) systematic review assessing saturation
in qualitative research, saturation can be reached within 25 interviews. As such, this study was
aiming to interview 20-25 participants as this number allowed for a relatively heterogenous
sample while still allowing for depth in individual experiences to be analyzed and shared
(Paggett, 2012). Participants were asked about their mental health, substance use, any
experiences they had accessing mental health services, and the impact of COVID-19 on mental
health, service utilization and substance use. As the data were being collected and analyzed
during the same time period, data collection was completed when there was a saturation of
themes among the interviews.

Data Collection
Procedure. Once participants expressed an interest in the study, they were sent a
Qualtrics survey with the consent information and a short demographic survey (Appendix B).
Participants identified a time to schedule the interview with the researcher which was then
conducted online over Zoom. Prior to the interview, the participant was sent the interview
questions. The interview time varied greatly depending on how many experiences participants
had accessing mental health services and ranged from 30 to 80 minutes. The interview guide is
available in the appendix (Appendix C). The interview covered the following topics:
understanding mental health problems and any substance use, experiences with accessing mental
health services, barriers to accessing services, what the participant considers helpful mental
health supports, and the impact of the pandemic in all these experiences. The interview was
recorded through Zoom and then stored on a secure OneDrive folder. After the interview was
over, participants received an electronic gift card as their honorarium as well as a resource sheet
with mental health supports in the GTA.
Establishing the Quality of the Data
The quality of the data was established through several means. According to Whittemore,
Chase, & Mandle (2001), credibility and authenticity in qualitative research is established when
the research reflects the experiences of participants. Sustained engagement with the participants
throughout the research process helped ensure that the research reflected the experiences of
participants. For example, following the creation of the interview transcript, participants were
sent their transcript to review. This gave participants space to clarify points in the interview as
well as ensure that participants were still comfortable with the information shared. Only one
participant responded with changes to the transcript. Afterwards, during the data analysis stage,

participants were engaged again to participate in one-to-one member checks. Overall, seven
participants participated in the member check. Participants reviewed the themes identified,
addressed gaps, and formulated recommendations for service providers (see Future Directions).
Participants discussed if the themes identified resonated with their own experiences, whether any
theme was unclear or confusing, and if they felt any information was missing. This process helped
ensure that the main findings from the data resonated with participants and accurately described
their lived experiences.
Data Analysis
Thematic analysis. All interviews were audio-recorded through Zoom and transcribed
verbatim. Transcripts were coded using NVivo qualitative research data analysis software
Version 12. Using Nvivo, transcripts were coded and organized into themes and subthemes. The
present study used thematic analysis outlined by Braun & Clarke (2006). Thematic analysis
involves identifying and reporting patterns within the data (Braun & Clarke, 2006). As Braun &
Clarke (2006) explain, this form of analysis aligns with constructivist thinking as the themes
identified from the experiences of participants reflect “the sociocultural context, and structural
conditions, that enable the individual accounts” (p. 85). Thus, the thematic analysis was part of
the meaning making process that both the researcher and participants were engaged in. The
analysis was completed using the six steps outlined by Braun & Clarke (2006). The first step
involved familiarizing myself with the data which involved transcribing and reading the data and
noting down initial thoughts and common experiences with a number of memos (Braun &
Clarke, 2006). The next steps involved generating initial codes and searching for themes among
the codes (Braun & Clarke, 2006). Next, definitions and names for the themes were identified

(Braun & Clarke, 2006). The final step involves the final write up of the themes (Braun &
Clarke, 2006).
The thematic analysis conducted for this project was a combination of inductive and
deductive approaches. While themes were identified from the data inductively, as Braun &
Clarke (2006) note, a researcher cannot be completely free from theory or background literature
and as such, the adapted AsianCrit framework provided certain sensitizing concepts that guided
thematic analysis such as themes and subthemes that focused on the impact of race on accessing
mental health services.
It should be noted that in identifying patterns from the data, I have inevitably generalized
the experiences of South Asians. While South Asians may come from the same geographical
region, their countries are very different. This is not simply a difference in language or customs,
but rather these countries have vastly different sociopolitical histories which include violence and
discrimination amongst each other. In conducting a thematic analysis, I work under the
assumption that, despite the heterogeneity of this population, experiences with mental health
problems and service utilization in the Canadian context will be similar because of similar
racialization processes explained by Iftikar & Museus (2014).
Ethical Considerations
This project was approved by the Research Ethics Board of Wilfrid Laurier University
(REB#6971). As this project is working with individuals who may experience increased
marginalization due to issues of race, gender, age, and mental health problems, several ethical
considerations were made. Racialized communities have experienced a history of mistreatment in
psychological research which has left many hesitant and suspicious of participating in research

(Williams, 2005). In order to overcome any hesitancy, I made the research objectives clear prior
to the interview and during the interview. Rather than playing the role of the interviewer, I played
the role of a peer as I am also a South Asian youth who has experienced mental health problems.
This involved using informal language and sharing my own experiences when appropriate
throughout the interview. This resulted in the participants leaving the interview on a positive note
as many said they enjoyed having the conversation and were glad that importance was being
placed on the mental health of South Asians.
Additionally, as this project dealt with sensitive topics such as mental health and
substance use, it was possible that the interview questions may put participants in a vulnerable
position as they may potentially discuss negative experiences that have arisen as a result of
mental health problems. Participants were provided with the interview questions prior to the
interview to ensure that they had time to review the questions and make clear if there were any
questions they wanted to skip. When asking participants at the end of the interview if they felt
distressed or required support, all the participants reported that they had a positive experience
from the interview, however steps were established if a participant felt overwhelmed or negative
during the interview, including providing them with the space to talk through their feelings,
ending and/or rescheduling the interview, and checking in with the participants afterwards to see
if they required further support.
A resource sheet with mental health and substance use resources was also provided after
the interview. Even if participants are not in a vulnerable position, this may still be useful as our
conversation is around access to mental health services. Participants may have expressed interest
in seeking out mental health services and so, a document listing mental health services serving
racialized communities and/or youth in the GTA was provided.

Another important step to ensure that the process of consent remained continuous was to
encourage participants to review and edit their transcript. This allowed individuals to make
clarifications or remove parts they no longer felt comfortable discussing, thus ensuring that there
was still an informed consent even after the interview was completed. Additionally, member
checking after the data analysis process also helped ensure that participants were comfortable
with the outcomes of the project.
Finally, participating in this study may have risked the personal privacy of the
participants. Several steps were taken to ensure informed consent about the risks associated with
the study and minimize this risk when possible. Firstly, participants were made aware of this risk
through the consent form and explanation of the project. As the interviews were taking place over
Zoom, participants were given an oral explanation of the study and had a summarized version of
the consent form read out loud (see Appendix C for interview guide and script). The full consent
form was provided ahead of time prior to the interview. Additionally, participants were told they
could skip any questions or end the interview at any point. There was also allotted time during
the interview for the participants to ask any questions. During the data collection and analysis
stage, transcripts of interviews were coded such that participants remained anonymous
throughout the process.
Positionality
I am a South Asian woman who has experienced mental health problems and also felt the
inadequacy of the mental health services I sought. By exploring my own mental health and
furthermore my cultural background, which I felt was never properly understood by the health
professionals I talked to, I began to realize that this issue I was facing was not entirely my fault.

The barriers I faced were not reflective of individual problems, but like every other aspect of
Canadian life, they were interwoven with larger systems of racism, white supremacy, and
neoliberalism. Thus, my own lived experiences allow me to enter this project with an
understanding of this issue beyond academia. That being said, I acknowledge that my
experiences are only my own and that many other South Asian youth have had experiences vastly
different from mine including those with positive experiences of accessing mental health
services.
Reflection as a Peer Researcher
There are many strengths and limitations that came from being a researcher working with
people who share similar social identities and lived experiences as myself. Being a peer assisted
in building rapport with participants and allowed for trust in the research process. There was an
implicit understanding that I would understand the experiences of the participants, often seen
when participants start their responses with “you probably know this…” or “you know how it is.”
Having this understanding of participant’s experiences was especially important in this current
study as one of the greatest concerns participants expressed when accessing mental health
support was feeling like their experiences were not well understood. It became clear when
participants stated that they had a positive experience from participating that providing a
welcoming and understanding space for participants to discuss their mental health and
experiences with mental health services was valuable in and of itself.
However, there were drawbacks in the research that came from sharing so many similar
experiences to the participants. Primarily, as a peer, there may have been times when I was not
appropriately probing for information because I have made implicit assumptions based on my

worldview as a South Asian. While this does not necessarily mean that I misunderstood a
participant’s experience or imposed my own ideas onto the participant, it does leave gaps in the
data analysis stage where certain subjects could have been elaborated on. For future studies, this
problem may be resolved by ensuring the interview guide has more detailed probes and having
pilot interviews. Additionally, this challenge is reflected in any knowledge mobilization piece, as
I have to step back from my experiences and knowledge as a South Asian to describe what the
findings of this project mean to someone who is not South Asian. This was done by having my
supervisor and other researchers who are not South Asian review my results and provide
feedback.
Results
Overall, 20 South Asian youth were interviewed to discuss their mental health
experiences and any experiences they had accessing mental health services. Table 1 shows
demographics of participants using descriptive statistics. Participants were South Asians between
the ages 16-27, identifying as experiencing mental health problems, residing in the Greater
Toronto Area, and English speaking. Participants self-identified as being part of various South
Asian ethnic groups including Sri Lankan, Indian, Pakistani, Gujarati, Bengali/Bangladeshi, and
Sikh. Majority (80%) of participants identified as women, 10% were men, and 10% were gender
queer or gender non-binary. Participants ranged from 16 to 27 years old with the average age of
participants being 24 years old. Majority (80%) of the participants were born in Canada or grew
up in Canada (in other words, arrived in Canada before the age 10).
Table 1 Demographic characteristics of participants (N=20)
Variable %

Gender Identity
Woman 80%
Man 10%
Gender Queer/Gender Non-binary 10%
Age
17-19 5%
20-27 95%
Country of Birth
Canada 50%
South Asian Country (e.g., India, Pakistan, 50%
Bangladesh)
Arrived in Canada before the age 10 30%
Arrived in Canada after the age 10 20%
Almost all the participants had accessed some form of mental health support with majority
(65%) of participants having had accessed university mental health services. Other mental health
services include community organizations and private mental health services offered through
participants’ workplaces. Overall, six themes arose from the interviews based on experiences
accessing mental health services and the impacts of COVID-19. When discussing facilitators and
barriers to mental health services, three themes arose from conversations: 1) a lack of diversity
among service providers, 2) difficulties building and maintaining relationships with service
providers, and 3) compounding mental health stigma. Next, when discussing the impacts of
COVID-19, the following themes arose: 4) the impact of the pandemic on mental health, 5)
substance use, and 6) accessing mental health services during the pandemic.
“Having someone that, you know, looks a little bit like you does help (008)” –A Lack
of Diversity Among Service Providers
Nearly all participants discussed a lack of diversity among the service providers they have
met. Accessing mental health services that predominantly involved White service providers
contributed to feelings that mental health services were not well equipped to assist South Asians.

Participants discussed that the prevalence of White service providers results in an emphasis on
Western beliefs and values ultimately leading to difficulties in the therapeutic session and the
extent to which participants felt connected and understood by their service provider. When asked
about their experiences seeking mental health services, one participant stated: “When I look at
them for myself, I can’t confidently say that I’ll access them just because like, I don’t think they’re
going to understand where I’m coming from.” (015) This uncertainty of not being understood by
service providers ultimately led the participant to not seek out services for several years. While
the participant did eventually seek out mental health services, it was only after they felt their
mental health had further worsened.
Explaining Your Culture. A consequence of the lack of diversity among service providers
is that South Asians are often required to explain the cultural context in which their experiences
are situated. Participants discussed how a lack of understanding or opportunity to discuss the
cultural norms or traditions that can influence their experiences can lead to service providers
misunderstanding or potentially judging them. Additionally, some participants described that this
process of unpacking cultural norms and values can be difficult and emotionally laborious,
ultimately taking away from the therapeutic session. For example, one participant stated:
It constantly feels like you’re … having to explain, like, not only your own issues, but also
your culture to kind of justify what you’re talking about, or like to justify your feelings, or
to explain why certain things are happening (019).
As the participant describes, this process becomes more about justifying their experiences
to a service provider than simply providing context to experiences shared during a therapeutic
session.

This process is further complicated when trying to navigate stereotypes as some
participants felt they had to rely on stereotypes to explain cultural norms or traditions: “you feel
like, pressure to like, qualify your statements … like, ‘oh, you’ve probably heard of this, you
know, stereotype’ …” (011) Using stereotypes to explain the South Asian culture can ultimately
paint a negative image for South Asians. Another participant discussed this dilemma and felt that
when they had to rely on negative stereotypes to explain their culture, they were reaffirming
Western beliefs of racial communities being less progressive than Western communities which
they wanted to avoid.
In contrast, many participants who had experiences with service providers who were South
Asian or persons of colour described feeling that their service provider understood where they
were coming from and expressed experiences as positive and helpful. One participant stated:
“For me, my therapist was actually like a brown woman. So, it was like this person clearly, like,
understood, like my background and like where I was coming from. So, I found that to be really
helpful” (012). Overall, this complex navigation that participants are made to do to ensure that
their experiences are properly understood or validated lead to overburdening the client and
provide less space for the service provider to offer support.
Incompatible Services. Another consequence of the lack of diversity among service
providers and resultant emphasis on Western values and norms is that various aspects of
accessing mental health services often do not align with the participants’ needs or expectations of
mental health support. This manifested in many ways including incompatible therapy modalities,
issues with the assessment process, and receiving unhelpful support from service providers. As
mentioned, majority of participants accessed mental health services through their university,
however many participants described how university mental health services were incompatible

with what they felt they needed. Some universities offered group support services where
participants described not feeling comfortable discussing personal issues or feeling like their
issues did not come up in group discussions. Additionally, services such as cognitive behaviour
therapy offered in universities did not give participants space to discuss family problems or
culture which they felt would have been helpful for them. For example, one participant stated “It
didn’t feel like an actual like, session. It just felt like I was in a classroom learning about things
that I should have known beforehand” (005).
Beyond issues with the types of services offered, issues with the incompatibility of services
trickle down to how service providers support participants throughout the assessment process and
therapeutic sessions. Service providers failed to recognize issues such as mental health stigma
which make it difficult for participants to answer questions regarding family history of mental
illness, a question that commonly occurs in mental health assessments. One participant described
their frustrations during the assessment stage as follows: “’The symptoms showed up for you
when you were 14-15. Are you sure there’s no [family] history?’ And I was like, Listen, lady, I
told you three times. We don’t talk about this.” (003)
Likewise, some participants discussed that during therapeutic sessions, service providers
often provide unhelpful advice or suggestions to participants. This is primarily seen in
discussions around family dynamics. The majority of participants discussed their family as a
source of mental health stress, however when discussing family issues to service providers, the
advice provided by service providers are often not feasible for most South Asian families. For
example, many service providers stated that clients should openly communicate with parents on
why their behaviour is harmful. Participants described the difficulty of receiving this kind of
advice from service providers: “they might just say that, ‘why don’t you just talk to your

parents?’ Simple as that. But it’s not like talking to them about mental health – it’s just not
something that has really ever occurred” (015) and “the counselor would give me like ideas on
things to do but they just seemed like impossible to do in my family” (018). Finally, when service
providers were met with conversations that were far removed from their own experiences, such
as conversations around race, culture, or religion, there seemed little attempt to address the
participants’ concerns. For example, one participant stated: “when I talked about my internalized
racism with my therapist in Guelph, we never brought it back up … I don’t know if it was like,
because I’ve been seeing her sporadically, or she just had no idea what to do with it.” (003)
In contrast, one participant who spoke with a racialized service provider stated: “They were
still able to kind of provide that competency and really have that understanding … in terms of
like, family dynamics and stuff like that.” (017) Speaking with a service provider who had shared
social identities with participants, for example a service provider who was South Asian or a
person of colour, who knew where the participant was coming from, allowed the participant’s
concerns to be understood and created a space where the service provider was better able to assist
the participant with their needs.
Intersecting Identities. Another challenge regarding the lack of diversity among service
providers discussed by participants is the increased difficulty experienced by South Asians who
experience further marginalization due to other intersecting identities. In particular, a number of
participants who identified as Lesbian, Gay, Transgender, or Queer (LGBTQ+) discussed their
difficulties in finding a service provider who understood their unique experiences as a South
Asian queer individual. These participants noted that discussing family dynamics or experiences
with race or culture are already difficult and not often well received by service providers and so,

this problem is further complicated when participants also discuss issues such as homophobia
within the family.
Participants discussed a desire to find a service provider who was a person of colour and
also queer friendly. As one participant described: “when I was going to racialized therapists,
there wasn’t really that intersection of queerness that I needed” (012). However, given the lack
of diversity among service providers, it is difficult to find a service provider who is able to meet
these criteria, and this often led to participants compromising and choosing what they felt was
more important for them at the moment. These participants described that this feeling of
compromising makes it difficult for participants to bring themselves fully into a therapeutic
session and ultimately can lead them to changing service providers to continue looking for one
with the specializations they require.
“I think the hardest thing was to find someone … that was able to understand my
concerns and just… hear me out.” (008) – Difficulties building and maintaining a
therapeutic relationship with service providers
Another major barrier discussed by participants in accessing mental health services is
building rapport with service providers and being able to maintain a therapeutic relationship.
Firstly, many participants encountered difficult experiences with service providers which
prevented rapport building. Next, participants who are interested in a therapeutic relationship
with their service provider are faced with additional barriers in acquiring regular therapeutic
sessions.
Feeling Unsupported by Service Providers. Many participants discussed difficult
experiences they have had with service providers. Participants described several negative

experiences including feeling like their concerns were being dismissed as well as feeling
unwelcomed or judged by their service provider. Participants attributed this dismissive behaviour
to their young age or ethnicity. For example, some participants felt that their opinions or
perspectives were dismissed when it came to receiving a diagnosis for their mental health
problems. When discussing the process of being diagnosed with ADHD, one participant stated:
“When I asked to be medicated, I was told, ‘Oh, you need to just wait. Like, I don’t think you
have ADHD.’” (015) The participant attributed the service provider’s dismissal as a result of
service providers having little experience working with racialized youth: “They’re dealing with a
community that hasn’t talked about it. So, when they get a young person to talk, talking about
mental health, it’s like, what do we do?” (015).
Another participant also discussed their difficulties in receiving a diagnosis of depression:
“So, she was like … your symptoms aren’t strong enough to be clinically to be diagnosed as like,
you know, depression … then she looked really agitated, like, I was wasting her time.” (017) As
illustrated by the quote, the participant struggled to have the service provider affirm their mental
health concerns as the service provider did not acknowledge the severity of their symptoms. This
participant also attributed the difficulty receiving a diagnosis as a result of a lack of support for
racialized communities. They further explained: “It really kind of made me realize, like, how
much how the current mental health services we’re really lacking in terms of providing supports
to persons of color…” (017). Not only did this create feelings of frustration for participants, but
it also halted their attempts to begin managing their mental health issues by delaying further
support such as medication.
In addition to difficulties receiving mental health support through a diagnosis, many
described having negative experiences with service providers. For example, as one participant

stated: “… there’s the sense that I always get like, as if I’m wasting their time, and it’s really
frustrating” (017). Another participant discussed a service provider’s response to certain difficult
situations in the participant’s life: “… it was just hard when she would look shocked or like
visibly, like, alarmed because then you start feeling like they’re judging you.” (019). Perceiving a
negative reaction from the service provider ultimately led the participant to feel that their
attempts to discuss their problems were “pointless” (019) and stop meeting with their service
provider. The participant attributed the shock and judgement displayed by the service provider as
a result of not having an adequate amount of experience with racialized communities. They felt
this lack of experience made the service provider react negatively to experiences shared by the
participant that were far removed from their own expectations or experiences. Overall, being met
with this lack of support made participants begin the process of seeking out new services or stop
seeking out services altogether.
In contrast, participants who felt heard and understood by service providers described the
positive experience they had. One participant stated: “And, you know, she didn’t pressure me to
do anything. And she was just so validating. And I just felt very seen and safe with her which was
really important.” (006) Participants understood that they were not always going to find a service
provider who had similar shared identities or experiences as their own, but it was important that
despite any differences, service providers were able to meet participants where they were at. For
example, one participant stated: “He didn’t judge me based on like, where I’m coming from, or
what my values are because obviously … his values and my values are completely different.”
(009)
Financial barriers and long wait times. In addition to building a therapeutic relationship
with a service provider, participants also discussed difficulties with maintaining this relationship.

Participants discussed the unaffordability of many mental health services and the issue of long
wait times, which reflect problems with Ontario’s mental health services, as a whole. They
mentioned that these two issues often go hand in hand as free mental health services, rather than
private practice, tend to have longer wait times due to higher demand. Majority (85%) of the
participants have had experiences accessing or on a waitlist to access publicly-funded services or
university services covered under student insurance. The remainder of the participants accessed
mental health services through work benefits.
Many participants experienced a long wait time when trying to access a mental health
service, whether it is accessing services for the first time or the time in between sessions.
Participants described waiting for months and up to years to access mental health services as well
as weeks in between appointments. Not being able to meet a service provider on a regular basis
created several issues for participants, including not feeling like they were able to build a
connection with the service provider or address their immediate concerns as they arose. They felt
that this not only reduced the effectiveness of the service, but also discouraged service utilization
as a whole.
This issue arose prominently for participants accessing university mental health services.
One participant described their experience accessing university mental health services: “And the
process took so long, they’re always always always backed up, which is, I think the one thing that
really … discourages students … just knowing that they don’t have space for you.” (005).
Beyond the university setting, participants discussed similar issues for drop-in centres where
there was no consistency with the service provider they met with: “… it was difficult to know
that I wasn’t seeing the same person again, like it’s hard to open up to one person.” (013)

Another participant stated: “When you’re not talking to someone consistently … I don’t find that
you’re building any rapport with them” (015) As the quotes illustrate, participants who were not
able to meet a service provider on a regular basis struggled to form any rapport with the service
provider. Without this foundational level of trust and comfort, participants expressed not being
able to have complex conversations around culture or family.
Hand in hand with the issue of wait times is the financial investment involved in meeting a
service provider on a regular basis. As a result, most participants discussed only accessing
publicly-funded services or accessing their university’s mental health services, where services are
covered under student insurance. As previously discussed, these services tend to have long wait
times and are often not structured to create lasting relationships with a single service provider.
Thus, participants are often in a difficult position where they are not being adequately supported
through university mental health services and not being able to afford other mental health
services. Participants who were not enrolled in post-secondary education also discussed the
financial barriers preventing them from accessing services. Most described requiring benefits
from their work to access mental health services: “… after university, I didn’t see a counselor
after that, because I wanted to kind of search for my own later on when I get a full-time job and
benefits for one.” (003). Another participant discussed work benefits as incentive for seeking out
mental health services: “Once I get those benefits, I feel like … I have a way bigger incentive to
be able to, like, you know, seek out that kind of help.” (001) Thus, costs associated with mental
health services were a big concern for participants as they either sought out free mental health
services or sought out service covered through work benefits.

Compounding Mental Health Stigma
Stigma was a prominent concern that all participants had to navigate, which had
implications for service access. While the participants themselves did not experience self-stigma
that made them wary or dubious of mental health services, participants did experience stigma
from those around them which negatively impacted their ability to access mental health services.
Based on the conversations with participants, there were three key areas where they experienced
mental health stigma. For some participants, stigma deterred them from accessing services and
for others, it created additional barriers to navigate when accessing services.
Family stigma. Stigma from family members, in particular participants’ parents, was a major
source of stress for nearly all participants. For example, one participant stated: “I have two
sisters like, yeah, they understand mental health, but like my parents don’t. So, it’s not something
that I can talk to them about.” (005) Participants described parents being dismissive of mental
health and distrusting of mental health services. Navigating this stigma often resulted in secrecy
around accessing mental health services as one participant states: “I need a way to leave here,
my house, to get there. Make up an excuse, because I, I will be honest, I do not want to tell my
parents.” (002) Additionally, many participants described the increased stress associated with
this secrecy: “I’d rather just like not deal with, you know, this uncomfortability. I’d rather just
like not go to therapy.” (012) These participants discussed that the additional stress associated
with accessing services whether it be making up excuses to leave the house or hiding medication
at home can ultimately outweigh the perceived benefits of service utilization and lead to
participants choosing not to access mental health services.
Cultural Stigma. Hand in hand with family stigma is the issue of cultural stigma. As one
participant stated: “I grew up in my community where mental health was a very taboo subject.”

(017) Many participants discussed the difficulties in navigating mental health within the South
Asian community where there was no space to talk about it. This can create issues within the
household as parents are wary of community members finding out about their children
experiencing mental health problems or accessing services. One participant describes the shame
associated with disclosing mental health issues to community members: “I was literally sat down
and said if anyone finds out from like, outside our home, it’s gonna … bring shame to our
family.” (015)
Similarly, one participant discussed how cultural stigma combined with gender
expectations made it difficult as a South Asian man to seek out mental health support:
So, it’s like, for you to be a man who’s South Asian and seeking this is like, even worse …
if you meet like a really outdated like, uncle or something, just, like, you know, ‘just go
out, like, be a man, like, you’re not supposed to complain or whatever.’ So that was like an
additional barrier.
Overall, the general stigma within the South Asian community further contributed to the
secrecy around accessing mental health services as participants did not feel like they could have
an open dialogue to discuss these issues.
Stigma Among Health Professionals. For many participants, their first point of contact in
terms of receiving mental health support was with their family doctor. However, many discussed
negative experiences they have had with family doctors when discussing their mental health.
Participants stated: “she was very, like, traditional in her idea that like, she’s like mental health
… isn’t real, but it can be solved with like, exercise and sunlight and stuff” (018) and “I recall,
talking to my family doctor, as well, and he was really dismissive … he was like, why do you

struggle with depression and anxiety? You’re such a young person, like you haven’t experienced
that yet.” Many participants discussed family doctors being dismissive of their mental health
and, as the second quote demonstrates, this was partly due to the fact that participants were
young. Experiencing this dismissal often led to frustration as participants had to find other
avenues of support including finding new family doctors and as a result, this often delayed access
to mental health services that required referrals from a family doctor.
Adjusting to Life During the Pandemic
Shifting now to the impacts of COVID-19 on the experiences of South Asians youth
experiencing mental health problems, many participants felt that the pandemic had worsened
their mental health. A number of factors contributed to the worsening of mental health including
the disruption of life events, staying at home more, and living in uncertain times.
Disruption of Transitional Life Events. The majority of the participants interviewed
were in their early 20s and described key transitional moments in their life such as starting new
jobs or graduate school, completing university, and moving out of their family home. However,
the pandemic had disrupted these transitional moments in their lives and as a result, participants
needed to navigate these new chapters of their lives while also responding to the pandemic. This
meant adjusting to working from home, attending virtual school courses, or not being able to
meet friends. For example, one participant described the negative impact of attending their first
year of university remotely: “I didn’t have the opportunity to meet new people, so I was stuck
with a lot of people from high school that weren’t good for me” (005). Navigating these changes
was difficult for many participants and negatively impacted their mental health.

Staying at Home. As a result of public health measures such as lockdowns, many
participants were staying at home more often with family members. Many participants described
increased friction with family members as a result of the increased time spent together:
… But then after a couple months was like, oh okay, now we’re just all in or like
everyone’s just up in each other’s like emotions and business and all these things started
popping up. That’s when I was like, felt like suffocated. (003)
As noted, family problems were often a source of stress for South Asian youth and so, spending
more time with family members can exacerbate the preexisting problems. Likewise, the
increased time spent at home often led to a loss of routine and social activities: “… university
was one of the places where I had a really big community, I have my chosen family. So being cut
off from that and stuck at home was definitely detrimental to your mental health.” (017)
Participants discussed that losing this system of support was very difficult for them especially in
conjunction with increased stress associated with being with family members more.
Increased Anxiety in an Uncertain World. Finally, many participants described an
increased anxiety associated with the pandemic and other current events. Anxiety around the fear
of testing positive for COVID-19 or family members testing positive, how long the pandemic
will last and job loss as a result of the lockdowns were described by participants. For example,
one participant stated: “The fear of the unknown was what really got to me like, when will this be
over? When will I be able to see my friends again?” (013)
Increased Cannabis Use Since the Pandemic
Participants were asked about alcohol and substance use and changes in consumption
associated with the pandemic. Participants who reported consuming alcohol described

consuming less during the pandemic. They described a decrease in social gatherings due to
public health measures such as lockdowns and this resulted in less opportunities for alcohol
consumption.
On the other hand, participants who reported consuming cannabis prior to the pandemic
reported an increase in cannabis consumption. Participants associated the increase in cannabis
consumption with a number of factors. Firstly, some participants described using more due to
boredom during the lockdowns: “it was more just to have something to do because it was so like
boring and like mundane just being at home in the summer.” (018). Next, consumption was also
associated with coping with anxiety and other mental health problems, for example one
participant described how smoking helped avoid overthinking and worrying about circumstances
in their life. Finally, participants described using cannabis to cope with work demands and
relaxation after work. Participants who had long and demanding work hours described how
cannabis use helped them stay focused or relax after work.
“I really didn’t reach out to my therapist, because I know I would have to hold a session at
home, and it wasn’t a safe space (017)” – Lack of convenience of remote services
When discussing the impact of COVID-19 on participants’ ability to access mental health
services, many expressed increased difficulties associated with service utilization during the
pandemic. While they appreciated the increased awareness of mental health during the pandemic,
they did not feel that the supports offered were adequate to addressing their mental health
concerns. Many factors contributed to the difficulty accessing services during the pandemic
including finding services to access, difficulties accessing remote services, and problems with
remote services.

Navigating Available Services. A consequence of the pandemic, and in particular the
lockdowns, is that it became difficult for participants to reach out to mental health services. It
was unclear which services were still operating during the lockdowns. This often meant
participants were left with unanswered voicemails or emails. In some cases, mental health
services that participants accessed prior to the pandemic had shut down forcing participants to
look elsewhere for new services. Relatedly, participants who have preferences for in-person
services, phone services, or virtual services needed to navigate what their options were for any
particular organization offering mental health services. This can be difficult if participants are not
able to reach out to the organization. For example, one participant described this process: “…
There’s that headache of trying to figure out like, okay, do they do it on the phone, in person, on
Zoom? Do they use like something else other than Zoom? And just kind of navigating all of that
just feels like a lot of effort.” (010)
Difficulties Accessing Remote Services from Home. With the pandemic came the shift to
more remote services such as accessing mental health services through videocalls, phone calls,
and smartphone apps. Many participants discussed the difficulties in accessing services while
under the same household as family members. Due to family stigma, participants’ households
were often not a safe space to access mental health services which led to participants deciding
not to access mental health services or adjust how they communicate during their sessions. As a
participant discussed: “… During the initial months of COVID, I really didn’t reach out to my
therapist, because I know I would have to hold a session at home, and it wasn’t a safe space.”
(017) Likewise, as many participants identified family issues as being a major source of mental
health stress, participants described needing to speak quieter or avoid directly mentioning family
members during conversations with service providers.

Ineffective Remote Services. When discussing how participants felt about the shift to
more remote services as a result of the pandemic, most participants felt it negatively affected the
quality of services. Firstly, remote services, particularly those offered through the phone, can
make it difficult to build trust between the service provider and client. As a participant
mentioned: “I feel like you’re missing a lot of things through a phone call, like you’re missing a
person’s body language or facial expressions.” (005) Not being able to see the service provider
or see how they are reacting to what the participant says can make it difficult to openly discuss
sensitive topics.
As a result of the pandemic, there has also been an increase in mental health smartphone
apps and participants discussed these applications as being generally unhelpful. These apps tend
to be self-directed, and homework based with limited interactions with a service provider. One
participant described how they felt this was an issue:
Which I personally felt kind of, you know, went against like what I was looking for in
terms of therapy like you want like that, kind of like open-ended conversation where
you’re able to bounce ideas off of each other (005)
Finally, these applications provide limited space to discuss issues previously described as
important to them such as family or culture.
Discussion
The present study highlighted several areas of concern in the field of mental health that
pose barriers to South Asian youth accessing services. A lack of diversity among service
providers and difficulties building rapport with service providers can lead to negative
experiences for South Asian youth accessing mental health services. Further, financial barriers,

wait times, and mental health stigma can further create barriers to service utilization. These
barriers to service utilization often led to participants constantly switching service providers and
can ultimately lead to delayed mental health support and more lifelong mental health problems.
These barriers are further complicated when considering the effect of COVID-19 on the mental
health of South Asian youth and their ability to access mental health services. Overall,
participants reported a worsening of mental health and increased substance use since the
pandemic and described increased difficulties accessing remote mental health services during the
pandemic.
Barriers to Accessing Mental Health Services
The study’s findings suggest the need for improved mental health services for South
Asian youth. Consistent with previous findings, particularly those noted by Islam et al. (2017),
issues related to the lack of diversity among service providers, the emphasis on Western values
for mental health services, waitlists, and costs for services were all concerns emphasized by
participants. These findings also align with Bowl (2007), Inman et al. (2014), Li & Browne
(2000), and Memnon et al. (2016) who all highlighted problems associated with a lack of cultural
awareness as a key barrier to accessing mental health services for South Asians. In addition,
participants in the present study emphasized the importance of finding a service provider who is
welcoming and understanding. Participants felt that reaching out to service providers can be
daunting when clients are not sure how the experiences they share will be received and so, when
South Asian youth are met with this lack of support and unwelcoming environment, it can
reaffirm the idea that mental health services are not equipped to support South Asians.
Similarly, experiences participants had where service providers were dismissive of their
mental health and symptoms suggest generally dismissive attitudes service providers have

toward youth experiencing mental health problems. One study in Scotland by Buston (2002)
interviewed 32 youth (14-20 years old) regarding experiences discussing their mental health
concerns to a health practitioner and found similar results of the dismissive attitudes towards
youth from health professionals due to their age and the need to build empathetic communication
skills by practitioners with youth. Similarly, Byrne et al. (2021) studied the experiences of youth
(12-25 years old) seeking out support in emergency departments for self harm and found that
participants often described hospital staff as disinterested and dismissive. Notions that young
people do not experience serious mental health concerns can be detrimental to youths’ mental
health and willingness to seek out support. Further, participants attributed the lack of support
from service providers as a result of service providers not having experience working with South
Asian youth. Participants discussed that this can create barriers to help-seeking because there is
little incentive for them to pay for mental health services when there is no guarantee that their
service provider is going to be understanding of their concerns or create a welcoming
environment for them.
A key finding that arose from the interviews was the importance of university mental
health services as a resource for many South Asian youth. The majority of the participants
described having experiences with university mental health services and feeling unsatisfied with
them. Some literature supports the concerns participants expressed. Robinson et al. (2016)
surveyed 400 university students and found that majority (74%) of students reported being aware
that their university offered mental health services, but only 8% of students reported being likely
to access services and of the students who expressed mental health challenges, about 13% said
they would access mental health services. Similarly, Storrie, Ahren, & Tuckett (2009) described
stigma and feeling like service providers would not understand their concerns as major barriers

identified in a systematic review of 11 articles regarding university students accessing mental
health services.
However, there is very limited research on the experiences of racialized university
students and the extent to which university services are able to provide culturally sensitive
services, especially in the Canadian context. One study by Giamos et al. (2017) interviewed 41
students regarding their mental health and experiences accessing campus mental health services.
Similar to the current findings, Giamos et al. (2017) highlighted long wait times and a lack of
cultural sensitivity in services. Overall, the experiences of racialized students accessing campus
mental health support is a clear gap in current mental health research.
When it comes to the issue of stigma as a barrier to mental health services, contrary to
Arora, Metz, & Carlson’s (2016) findings that South Asian college students showed increased
personal stigma which discouraged help seeking behaviour, participants did not describe any
personal stigma that discouraged them from accessing mental health services. Instead, public
stigma, in other words the stigma from others around them, was often a barrier to accessing
mental health services. However, this may because the participants of this study are more
inclined to discuss their mental health as the recruitment poster for this project explicitly state
that the interview involved discussing mental health experiences. Thus, those who may hold
more stigmatizing views on mental health or stigmatizing experiences are less likely to
participate in this study. Similarly, it should be noted that Arora, Metz, & Carlson (2016) do
mention gender differences in personal stigma where women are more willing to seek mental
health services, and majority of the participants in the present study are women.
An important facet of public stigma is courtesy stigma which refers to how family
members may be stigmatized due to their affiliation with someone who experiences mental

health problems (Gary, 2005). Courtesy stigma can negatively impact the family member’s
reputation and status in the community (Gary, 2005). Stigma from family members and the need
to conceal family member’s mental health status often impeded participants’ ability or
willingness to access mental health services.
The present study suggests that more work still needs to be done regarding addressing
mental health stigma among South Asian youth including youth’s experiences with discussing
mental health in their culture and perhaps a deeper dive into the experiences of South Asian men.
For service providers, these dimensions of stigma should be acknowledged and addressed with
clients to find supports that are feasible for clients. As participants have made clear, experiences
with family and cultural stigma can make it difficult to have open conversations with family
members about problems that contribute to poor mental health and so, other avenues of support
should be sought out.
Substance Use
There is limited research on substance use among South Asian youth. Studies by Rastogi
& Wadhwa (2009), Bhattacharya (1998) and Islam et al. (2017) point to substance use being a
means to cope with mental health problems and integrate into North American culture. In the
present study, only the former was seen as participants discussed primarily using cannabis to help
cope with anxiety, stress, and work demands. Among participants who grew up in Canada and
those who moved to Canada at a later age, cannabis use was not perceived to be linked with
wanting to “fit in” with Western culture.
While participants did not describe their cannabis use as something that is negatively
impacting their life, in other words as misuse, it should be noted that the majority of participants

who used cannabis reported an increase in use since the pandemic. This aligns with the survey
conducted by Rotermann (2020) that reported increased substance use among Canadians who
reported poorer mental health since the pandemic. Similarly, Bartel, Sherry, & Steward (2020)
found that self-isolation and depression contributed to greater cannabis use. Thus, further
investigation on the experiences of South Asian youth should be conducted to better understand
the ongoing impact of the pandemic on substance use.
The Impact of COVID-19 On Mental Health & Service Utilization
Consistent with earlier studies by Rotermann (2020), CAMH (2020), and Moyser (2020),
participants stated that the pandemic has negatively impacted their mental health. Particularly,
the present study sheds light on Moyser’s (2020) survey that found that South Asians in Canada
reported the highest prevalence of self-rated poor mental health and anxiety since the pandemic.
While Moyser’s (2020) survey was not specifically focused on South Asian youth, the present
study suggests some explanation for the survey results as the loss of social support and increased
time spent at home with family members was found to be a major source of stress for South
Asian youth. Family obligations and conflict that South Asians experienced described by Islam et
al. (2017), Sharma, Shaligram, & Yoon (2020), and Rastogi & Wadhwa (2009) may have been
exacerbated during the pandemic, which can contribute to a worsening mental health. Aside from
increased conflict from increased time spent at home, the other issues that participants described
including navigating changes as a result of the pandemic and anxiety associated with the
pandemic point to a heightened need for effective mental health services for South Asian youth.
The present study provides critical insight on the current state of mental health services
during the pandemic especially the shift towards more remote services. A recent study by

Strudwick et al. (2021) reviewed digital mental health interventions and identified 31 mobile
apps and 114 web-based mental health resources (such as telemedicine, virtual peer support, etc.)
across Canada. Similar to the present study, the authors found that the digital interventions are
disadvantageous to people who do not have access to a private or safe space when accessing
remote mental health services (Strudwick et al., 2021). Further, they recognized the difficulty in
establishing a therapeutic alliance between service providers and service users as a barrier to
remote services. The current findings highlight a need to further investigate the effectiveness of
remote mental health services and the extent to which they are accessible for different
marginalized groups.
Returning to Asian Critical Theory
The present study is the first to apply an AsianCrit theory to understanding the
experiences of South Asians in Canada. The study highlights how systems of oppression such as
White Supremacy are subtly perpetuated in Canada’s mental health system. Issues of racial
inequity continue to contribute to poor experiences and barriers to accessing mental health
services (Corneau & Stergiopoulos, 2012). Participants from the current study struggled to
communicate and validate their unique experiences as South Asian youth to non-South Asian
service providers including issues around culture, family, and navigating their social identity.
Despite the willingness of many to seek out mental health services, many are left frustrated and
unsupported. These barriers to effective mental health support may be the result and further
perpetuate the feelings of otherness described by Iftikar & Museus (2014). As the authors
explain, Asians are often racialized as foreigners, and this results in Asians being systematically
excluded in Canadian health policy and programs (Iftikar & Museus, 2018). This includes mental
health services where we see that service providers are not well equipped to assist South Asian

youth. South Asian youth who are met with this lack of support may be discouraged from further
seeking out mental health support and likewise, may experience poorer mental health as a result
of their circumstances.
Other forms of racialization such as the model minority stereotype commonly attributed
to South Asians can also create an impact on South Asian youths’ ability to access mental health
services as this stereotype may be internalized by South Asian community members. Mental
health stigma exhibited by family members or the South Asian community may be a result of
attempting to uphold the model minority stereotype and lead to a concealment of mental health
problems (Arora, Metz, & Carlson, 2016). The perpetuation of this stereotype can ensure that
South Asians, while perhaps still considered foreigners, are at the very least considered
successful foreigners. When considering the double stigma described by Gary (2005), concealing
mental health problems and internalizing the model minority stereotype may be seen as a way to
deter discrimination that otherwise may come as a result of being South Asian and experiencing
mental health problems. However, this comes at the cost of leaving mental health problems
unaddressed and unsupported. In this case, the experiences of South Asian mental health and
service utilization speaks to a larger issue relating to difficulties navigating in a system that
favours White people.
Beyond the racialization processes described by Iftikar & Museus (2014), the authors
additionally describe the importance of re-constructing the collective Asian historical narrative.
We can understand this gap in mental health services for South Asians as a result of South
Asians being silenced for much of Canadian history. With the increase in Asian hate and
Islamophobia, there is a need to raise the voices of South Asians (Lee & Jang, 2021). The present
study makes a small step towards highlighting the voices of South Asian youth in the context of

mental health service utilization. Further recognition needs to be made of the experiences of
South Asian youth who represent diverse social identities including gender, sexuality, and
disability. For example, findings from the present study suggests that queer South Asian youth
face unique challenges to accessing mental health supports and often feel that they are
compromising parts of their identity when seeking help, for example they may not disclose their
sexual identity when talking to service providers who do not offer a specialization in LGBTQ+
issues.
Overall, the mental health concerns and barriers to accessing mental health services
described by participants in the present study can be understood when acknowledging the
difficulties in navigating White Supremacy. Excluding South Asian voices from Canadian history
has led to mental health services that are ill equipped to address the concerns of South Asians
leaving many to constantly seek out new service providers or avoid service utilization altogether.
Addressing this service gap will involve both program and systemic level changes in the ways
that incorporate South Asian voices into research, programs, and policy.
Future Directions
Nearly all the participants who accessed mental health services sought out mental health
services at their university’s wellness centre and likewise, almost all the barriers described by
participants were experienced in these settings. There is a great need to improve the capacity and
quality of care provided by universities as it is often the first time youth are accessing mental
health services and likewise, it is often the only viable option for them due to financial barriers.
Hiring more mental health support workers particularly those with diverse backgrounds,
providing adequate training to workers to support the university’s diverse population, and

providing students with autonomy to choose their service provider are key ways in which
universities can improve the quality of the services they provide.
Beyond university service settings, there is an increased need for more information and
awareness of mental health services that better address the needs of South Asian youth. Social
media can potentially be a powerful tool for increased knowledge of the diverse types of mental
health services allowing youth to search for the kind of mental health services best suited for
them, whether it is finding a service provider who is a person of colour, queer friendly, or offers
other forms of specialization, or options for low cost/free mental health services. Participants
discussed existing social media accounts that share information regarding South Asian mental
health, however there is still a need for a repository of local services and service providers.
The current study also highlights key areas of interest for future research. As mentioned,
research taking an intersectionality lens should continue to explore the experiences of LGBTQ+
South Asians and their unique challenges finding a service provider that meets their needs. The
findings from the current study show that LGBTQ+ South Asian youth often have to compromise
themselves to access mental health services and rarely are able to find service providers who are
queer friendly and have the cultural understanding they require.
Next, research suggests that issues around mental health stigma may be different for
South Asian men than women and so, future research should explore how personal or public
stigma may influence service utilization among South Asian men. While the current study
comprised of mostly women participants, insights of the men participants does suggest that
gender expectations can further contribute to mental health stigma and prevent service
utilization. Similarly, family stigma was a major barrier for youth and often led youth to only

access mental health services once they were enrolled in university and likely better able to
advocate for themselves. Understanding how to reduce family stigma and incorporate parents
into the process of youth accessing mental health services can be an important avenue to study
and seek change in order to reduce more lifelong mental health problems.
Further, the current project focuses on the experiences of participants in the GTA,
however experiences of South Asian youth may differ elsewhere in Canada. In particular, as the
majority of South Asians live in Ontario and British Columbia, exploring the state of mental
health services in British Columbia may result in different experiences (Statistics Canada, 2007).
Exploring these geographical differences may have implications for the kinds of services that
best meet the needs of South Asian youth.
Finally, while the current study attempted to look at how Canadian born and immigrant
South Asian youth may have different experiences accessing mental health services, the number
of newcomer South Asians interviewed was limited. Similarly, when looking at the experiences
of these groups, there were no unique experiences among those born and raised in Canada and
those who recently immigrated to Canada. Thus, future research should continue to work with
these subgroups to explore potentially unique needs and experiences of Canadian born and
immigrant South Asian youth.
Recommendations for Service Providers
While grand, systemic changes may not always be feasible, service providers are also able to
make their own personal changes to improve the quality of support they provide to South Asian
youth. Below is a list of recommendations provided by participants to service providers, and the
service organizations in which they are based, on how they think their experiences with service

providers can be improved. These recommendations were provided during the interview and
member check with participants. Service providers should:
1. Practice compassion and non-judgement and create affirming and empowering spaces for
clients so that they feel valued, and their needs and concerns are also valued.
2. Understand and implement an Anti-Racism/Anti-Oppression framework into practice in
order to better understand the realities of South Asians navigating in systems of
oppression such as White Supremacy and Colonialism.
3. Be transparent about what they can and cannot help clients with, being clear about their
own beliefs, values, and specialization.
4. Create a co-learning environment with the client and provide space for them to ask
questions. It’s okay to say: “I need to learn more and I’m willing to learn with you.”
5. Recognize the intersection of identities that South Asian folks may have including
disabilities, queerness, gender, and other complex identities and how this contributes to
their experiences.
6. Explore different kinds of therapeutic supports with South Asians such as narrative
therapies and brave spaces.
7. Practice cultural humility and cultural safety. Cultural humility involves recognizing their
own positionality and biases and building active reflection into practice while cultural
safety involves respectful engagement with clients where clients feel safe when receiving
services (FNHA, n.d.)
8. Never leave a client empty handed. If it is not possible to take a client on, provide them
with other resources they can access and take the time to learn about other service

providers in your service network that may be a better fit for clients you are not able to
support.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.

Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the

pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the

participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of

service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.

Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of

participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English
may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings

can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings
related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.

Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.
Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors

can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.
Limitations
Time constraints and undertaking the project during the COVID-19 pandemic, in
particular during the Omicron variant wave, created various limitations regarding participant
recruitment. Firstly, the extent to which Access Alliance was able to assist in the recruitment of
participants was greatly limited and thus, potentially limited the ability to hear from service users
from Access Alliance. As Access Alliance is an organization that focuses on assisting
marginalized communities including the South Asian community, conversations with their
service users may have yielded more information on ways to facilitate access to mental health
services. Further, while the project attempted to explore the experiences of a diverse group of
South Asian youth for the study, majority of participants were over 20 years old, women, and
born/raised in Canada. Time constraints for the project prevented more strategic approaches to
recruit more South Asian men, younger youth and immigrant South Asians. Further, most of the
participants were currently enrolled in or graduated from university. This sample may be
privileged in ways that South Asian youth who do not have a university background are not.
Next, the experiences of South Asians with intersecting identities and how this contributes to
accessing mental health services was not extensively explored. Similarly, projects such as this
invariably generalize the experiences of South Asians when in reality, the cultures, religions, and
history of South Asians are heterogenous and may result in different experiences with mental
health, service utilization, and stigma. Finally, the study eligibility requirement to speak English

may have created barriers for newcomer/immigrant South Asians who may be experiencing
mental health problems.
Knowledge Mobilization Plan
The long-term goal of this project, and any future studies, is to increase access to mental
health services for members of the South Asian community by: 1) reducing mental health stigma
and 2) tailoring mental health services to better fit the needs of South Asian individuals
experiencing mental health problems. The current research project is the first step in exploring
and identifying barriers to mental health services with this subgroup of South Asians. Findings
can begin to inform service providers about the ways in which mental health services are not
meeting the needs of South Asian youths so that alternative solutions that better align with these
needs can be planned, funded, and implemented. In order to inform action, several knowledge
mobilization approaches will be used including presenting in conferences, sharing community
reports, sharing findings on social media, and publishing the findings in an academic journal.
Presentations. In working with Access Alliance, findings of the project will be presented
to members of the organization. Audience members will include Access Alliance’s network of
service providers, community mental health researchers, and service users. The presentation will
be an opportunity to share key findings including the recommendations shared by participants.
Additionally, presenting findings in Community Psychology conferences as well as mental health
and/or youth focused conferences hosted by non-profit organizations. This allows the
dissemination of knowledge to researchers and mental health service providers.
Community Reports. In addition to presenting findings, two community reports
highlighting the key points of the study have been created. One report highlights the findings

related to barriers accessing mental health services among South Asian youth (Appendix D)
while a second report focuses particularly on the experiences of South Asian youth during the
pandemic (Appendix E). Creating two separate documents avoids having the reports become too
long and allows for the distribution of this knowledge in different spaces. For example, in
conferences or knowledge exchange events that focus specifically on the pandemic, the
community report focused on the impacts of COVID-19 on South Asian youth is more relevant.
The community reports will be shared with Access Alliance during the presentation.
Additionally, the reports will be shared with the participants of the study.
Social Media. Social media can be a powerful tool to share information and has already
proven to be helpful in participant recruitment for this study. Thus, it will be a useful space to
share information about this project with South Asian youth and organizations focused on mental
health, youth, and/or racialized communities. Key points from the background literature, results,
and discussion including recommendations to service providers will be made into posts and
shared with other Instagram accounts following the submission of the thesis. Linking these posts
to the community report will also allow for greater distribution of the report.
Published Paper. Finally, I intend to publish my findings in an academic journal. This
project can further knowledge in the field of community mental health as it addresses the mental
health concerns of a marginalized group and decenters Western conceptions of mental health. It
is important that this kind of knowledge reaches an academic audience as it can be a driver
towards more qualitative research with members of the South Asian community. Additionally, as
mentioned in the Future Directions, the current findings of the project have suggested new
avenues for research including further exploration of the mental health experiences of LGBTQ+
South Asian youth, university mental health supports, and remote mental health services.

Conclusion
While there is growing research and awareness on the mental health experiences of South
Asian youth, the present study demonstrates that more still needs to be done. Findings suggest
that South Asian youth are experiencing several barriers to accessing mental health services. In
particular, the current findings suggest a need for increased diversity among service providers,
creating supportive environments for clients, and addressing financial barriers and wait times as
necessary steps to improve mental health supports. Additionally, mental health stigma from
family members, the South Asian community, and health professionals such as family doctors
can create additional barriers for South Asian youth to navigate. These findings present new
avenues to explore in the context of research and program development in order to better meet
the needs of this population.

