


1
Chapter 1: Introduction to the Study
Introduction
The emerging pandemic growth rate of people with diabetes in India is causing
major concern (Sierra, 2009). This study evaluated the feasibility and desirability of an
integrative approach combining modern and traditional systems of medicine in India to
address the enormous challenge posed by the emerging pandemic growth rate of diabetes.
According to the International Diabetes Federation (IDF; 2013), “Diabetes requires
culturally appropriate intervention in order to reduce the enormous personal suffering and
economic burden that grows with this epidemic” (p. 2).
In keeping with the cultural ethos of India, this participatory case study was an
attempt to add to the body of knowledge by addressing the public health challenge of
diabetes in India. Being a chronic disease, diabetes has lifelong consequences not just for
the patient and patient’s family but also for the entire healthcare system of a nation
(Cameron, Zimmet, Shaw, & Alberti, 2009). Specific to India’s health care system and its
ability to treat current and projected Type 2 diabetics, using the case study approach, I
evaluated the rationale for an integrative approach combining modern and traditional
systems of medicine. In this chapter, I provide the background of the study, followed by
an explanation of the traditional schools of medicine practiced in India. That is followed
by statement of the problem, purpose of the study, research questions, nature of the study,
research methodology, definitions, assumptions, scope and delimitations, and
significance of the study, ending with a summary of the chapter.

2
Background
IDF (2011) describes diabetes as not only a health crisis, but also a global societal
catastrophe. IDF estimates that the global population of people with diabetes is now
approaching 382 million. Diabetes, in the assessment of IDF, is at a crisis levels and
escalating. “Every seven seconds someone somewhere dies from diabetes, accounting for
4.8 million deaths globally each year” (IDF, 2013, p. 1). The number of people with
diabetes continues to grow and is on its way to crossing the half billion-population mark.
IDF projects that by 2035, the number of people with diabetes in India will increase to
101 million, accounting for about 20% of world’s burden of this disease (IDF, 2013, p.
12). Ramachandran and Snehlata (1999) described diabetes as the epidemic of the 21st
century.
Figure 1. Global incidence of diabetes. From Global Diabetes Atlas (6th ed.), by the
International Diabetes Federation, 2013. Retrieved from http://www.idf.org/sites/default
/files/ The_Global_Burden.pdf

3
The global health expenditure on account of diabetes is slated to increase from
$548 billion in U.S. dollars (USD) to $627 billion in 2035 (IDF, 2013).
Figure 2. Global expenditure on diabetes. From Global Diabetes Atlas (6th ed.), by the
International Diabetes Federation, 2013. Retrieved from http://www.idf.org/sites/default
/files/ The_Global_Burden.pdf
Deaths due to diabetes far exceed deaths due to HIV/AIDS, malaria, and
tuberculosis combined (IDF, 2012). The enormity of the challenge posed by diabetes and
its escalating treatment and management costs has led many governments to collaborate
with nongovernmental and private voluntary organizations (NGOs/PVOs). The collective
efforts of various agencies have been focused on measures to arrest the growth rate of
diabetes in their respective countries and areas of influence. These measures include
public awareness campaigns on diet and lifestyle with encouragement of a preventative
lifestyle (Das & Mukhopadhyay, 2011). IDF (2011) summarized the gravity of diabetes
4
in the following statement: “this disease is one of the century’s greatest health challenges
and remains on a relentlessly upward trajectory” (p. 1). Resource-challenged developing
economies like India can ill afford to carry such a large magnitude of chronic disease
burden (Sierra, 2009). Diabetes is the single most important health challenge in the
category of noncommunicable diseases globally (Ramachandran, 1992).
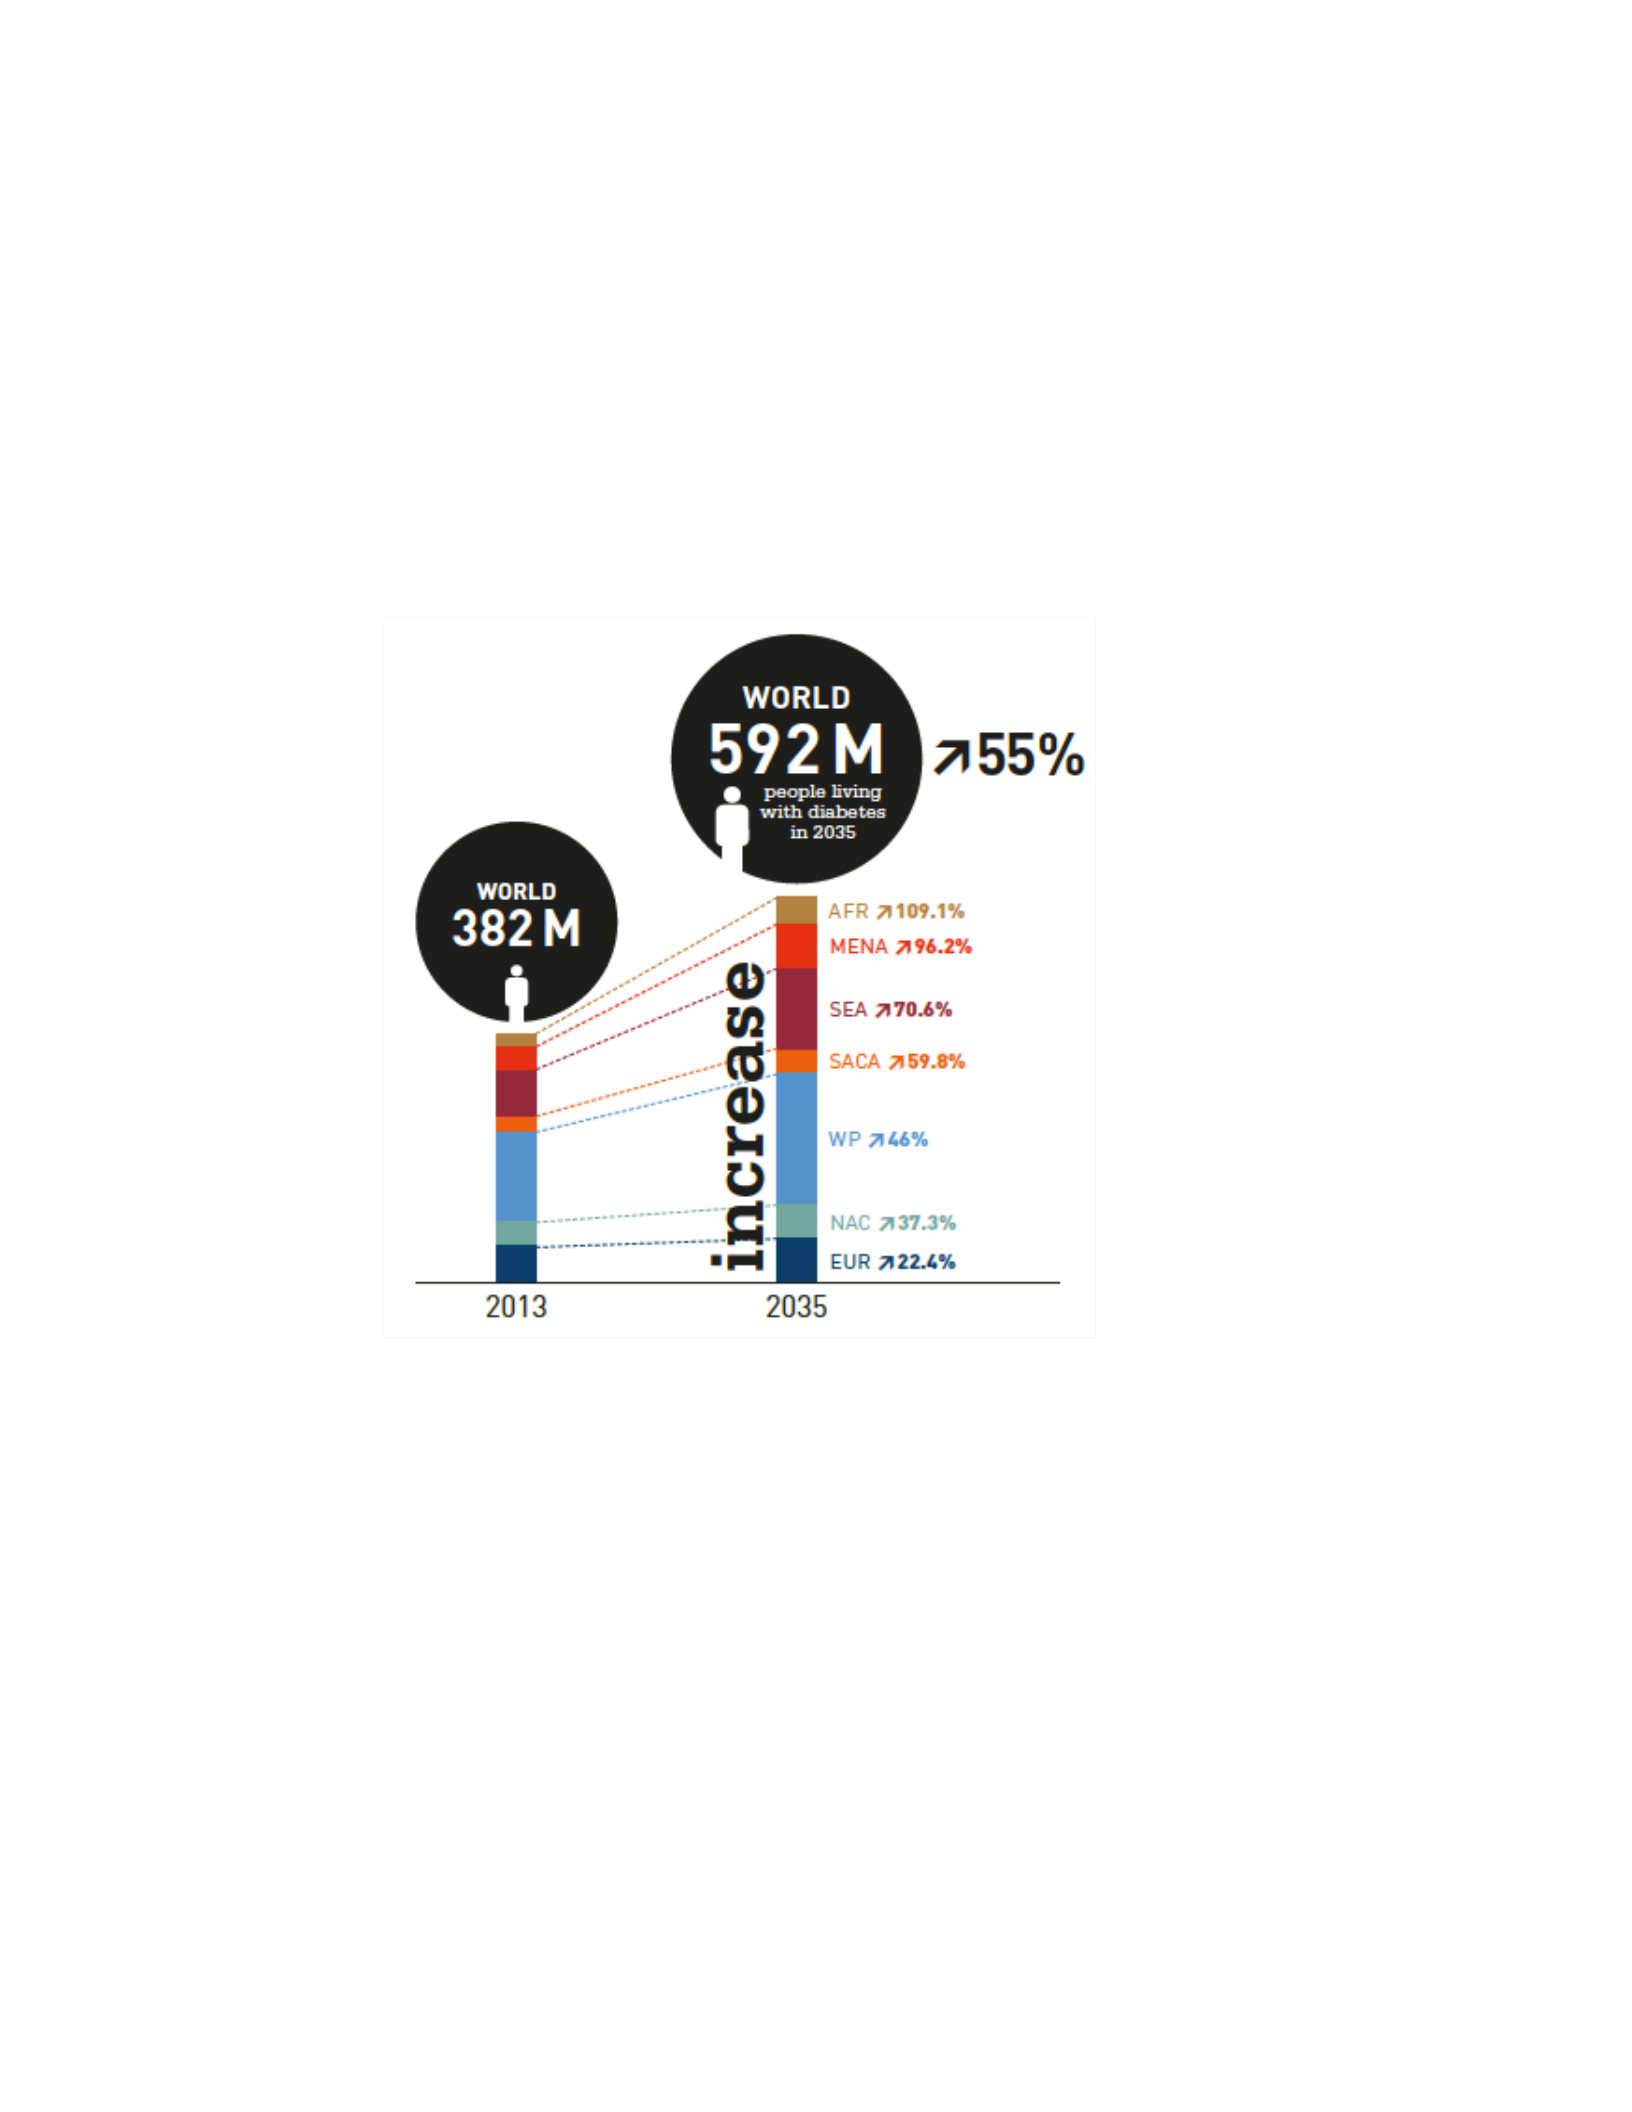
Figure 3. Projected increase in global diabetic population. AFR = Africa, MENA =
Middle East North Africa, SEA = South East Asia, SACA = South & Central Africa, WP
= Western Pacific, NAC = North America & Caribbean, EUR = Europe. From Global
Diabetes Atlas (6th ed.), by the International Diabetes Federation, 2013. Retrieved from
http://www.idf.org/sites/default/files/The_Global_Burden.pdf
Magnitude of Diabetes in India
Shetty (2012) described the enormity of the challenge in India in the article title
“Public Health, India’s Diabetes Time Bomb” (p. S14). India adds 5,000 people every

5
day to its population of diabetics (Diamond, 2011). It is imperative for India to do
everything possible to contain the alarming increase in the incidence of diabetes, which
has attained emerging pandemic proportions (Sierra, 2009). India is just behind China
both in population and in the number of people with diabetes, as shown in Figure 6 on
page 29.
Many initiatives have been launched both by the Indian government and by a
large number of national and international voluntary health groups and NGOs operating
in India. These include the Indian task force on diabetes (http://www.diabetes.india.
com/diabetes) and The National Program for Prevention and Control of Cancer, Diabetes,
Cardiovascular Diseases, and Stroke (NPCDCS; the program aims to screen 200 million
Indians for diabetes) and several other public and community health initiatives. The
global NGO Project HOPE, Indian NGO, and Diabetes Care India are examples of the
many agencies working in this area. Large global philanthropic institutions have also
come forward to find a solution for the enormity of India’s diabetes challenge (Kinra et
al., 2011).
Case study involves in-depth examination of people and groups of people. Using
the case study approach, I evaluated the emerging pandemic of diabetes in India.
Diabetes has posed a major public health challenge for the Indian population within India
and the worldwide Indian diaspora (Shetty, 2012). There is strong scientific evidence that
Indians have a greater degree of insulin resistance and a stronger genetic predisposition to
diabetes (Mohan, 2004). In the 1970s, the Indian Council of Medical Research (ICMR)
reported the incidence of non-insulin-dependent diabetes mellitus (NIDDM) in India to

6
be 2.3% in urban and 1.5% in rural areas (Ramachandran, 1992). Researchers of recent
studies both among Indians living in India and Indians living overseas have shown much
higher incidence of diabetes (Kinra et al., 2011). Balagopal, Kamalamma, Patel, and
Misra (2008) showed that the ratio of new diabetics to known diabetics was 1:2 in urban
and 3:1 in rural areas and that the incidence of diabetes in Indian males was significantly
higher than in females. IDF estimates that the incidence of nondiagnosis of diabetes in
India is as high as 51% (IDF, 2013).
The continued pace of urban migration, sedentary lifestyles, and changes in
dietary habits of Indians have added to the gravity of the problem. Diabetes, being a
chronic health condition, has serious and severe lifelong implications for the patient and
requires lifelong management. The onset of diabetes is preceded by a phase described as
prediabetes, also referred to as impaired glucose tolerance (IGT) condition (IDF, 2011).
It is estimated that over 32 million Indians are presently in the prediabetic stage (IDF,
2013). People with prediabetes should be prevented from getting diabetes (IDF, 2013).
NGOs in India are focused on campaigns to create awareness among people with pre-
diabetes so that they may avoid becoming diabetic. An NGO called Diabetes Care India
is running a campaign called KADAM (Knowledge Based Actions for Diabetes
Awareness Movement, Venkatraman & Mehta, 2011). In their study, Venkatraman and
Mehta (2011) noted the beneficial impact of these efforts.

7
Traditional Schools of Medicine in India
The World Health Organization (WHO) is cognizant of the importance and
potential of traditional systems of medicine in community life. WHO defines traditional
medicine as
medical knowledge systems that developed over generations within various
societies before the era of modern medicine, including the health practices,
approaches, knowledge and beliefs incorporating plant, animal and mineral-based
medicines, spiritual therapies, manual techniques and exercises, applied singularly
or in combination to treat, diagnose and prevent illnesses or maintain well-being.
(WHO, 2000, para. 1)
India is home to many native, and adapted, widely practiced heritage traditions of
medicine. The alternative traditions are of two types. Those of the first type originated in
India, such as Ayurveda, siddha and yoga. Those of the second type originated outside
India but are very widely accepted in India as indigenous. Examples of these are unani
(originated in Greece), homeopathy (originated in Germany), and sowa rigpa (originated
in Tibet). The alternative traditions have been practiced in India for thousands of years.
The Government of India recognizes six of these traditions as part of India’s mainstream
healthcare delivery process. These traditions are referred to in an acronym AYUSH—
Ayurveda, yoga and naturopathy, Unani, Siddha (a variant of Ayurveda), and
homeopathy and sowa rigpa. Due to the size and population of India, modern medical
facilities are not available in all parts of the country.

8
In the remote regions of India where modern healthcare facilities are unavailable,
people seek out and use traditional systems of medicine for all health conditions. India
does not have the requisite manpower and medical professionals to address a problem of
this scale and magnitude. Even where modern healthcare facilities exist, only 600,000
active practitioners of modern medicine cannot attend to all health needs of the people
and also give special attention to diabetes (Indian Medical Council Press Release, 2013,
enclosed as Appendix E).
The Ministry of Health & Family Welfare of the Indian government has a full-
fledged wing called the Department of AYUSH to regulate and promote the working of
these systems (http://indianmedicine.nic.in). In addition to the five main alternative
health traditions, there are others, such as Tibetan medicine and other herbal schools of
medicine, which are practiced in different parts of the country. In 2013, the Indian
Government added Sowa-Rigpa (also called Amchi) system of medicine under the ambit
of recognized traditional systems of medicine, AYUSH. With the addition of Sowa-
Rigpa, AYUSH now has six traditional systems of medicine. Despite the presence of an
impressive array of alternative health traditions, there has been little effort in India to
make the various schools of medicine work collectively and/or in unison to help contain
India’s diabetes emerging pandemic. This strategic gap was well confirmed in the search
and review of the scholarly literature on the subject. The available scholarly work alludes
to the potential of modern and traditional systems such as Ayurveda working together
with modern medicine (Rastogi, 2010).

9
There has been insufficient effort to enlist the support of traditional systems for
combating or addressing the public health challenge posed by emerging pandemics such
as diabetes, despite wide practice and penetration of traditional medical systems in India.
While there is no scientific study to establish the extent of penetration of AYUSH
services in India, the media estimates that 70% of Indians use AYUSH products and
solutions for their primary health needs (Public Broadcasting Service, 2011). Detailed
scrutiny of scientific literature has brought out that the potential benefits of such a
collaborative and complementary approach have been neither evaluated nor tried in any
significant structured manner. This study has attempted to fill a crucial gap in the
scholarly literature by investigating the desirability, feasibility, and potentiality of a
collaborative approach in addressing the challenge of diabetes in India.
Statement of the Problem
Epigenetics and lifestyle are conspiring to inflict a massive epidemic of Type 2
diabetes in the subcontinent (Shetty, 2012). The Indian government and public health
officials acknowledge the scale of diabetes problem in the country but have been slow in
implementing measures and initiatives to remedy the situation. In July 2010, the Indian
government launched a USD 230 million program for mass screening of Indians for
noncommunicable diseases such as diabetes. At the launch event, the Indian Federal
Minister of Health announced that 200 million Indians over the age of 30 would be
screened for diabetes in the first year. Soon after the launch event, the announced target
was promptly reduced to 70 million. The actual number of people screened as per Indian

10
news-press was estimated to be less than 20% of the reduced target (Ministry of Health
and Family Welfare, 2012).
The crux of the problem is that many of the medical professionals needed to
execute a program of this scale are not there. As per government records, only 693
medical officers out of a targeted 32,000 were trained in the rapid diabetes-screening
program. While the availability of medical professionals in urban India is a lesser
challenge, the problem in rural areas is nearly impossible to overcome (Ministry of
Health and Family Welfare, 2012). A review of the program revealed that ordinary
citizens were trained to implement the program. The initiatives are being well supported
by private voluntary groups. Sucre Blue, a Bangalore-based nongovernmental
organization, started a self-empowerment campaign and trained ordinary residents in two
villages outside the city of Bangalore to screen other villagers. Sucre Blue volunteers
were shocked to find prevalence rates of diabetes approaching a third of all adults
(Bergen, 2013).
The current methodology and resources deployed to contain the diabetes
emerging pandemic in India are inadequate and have not delivered the desired results.
These results are well beyond the capability and reach of the 600,000 active practitioners
of modern medicine (Indian Medical Council Press Release, 2013, enclosed as Appendix
E), as diabetes is just one among the many diseases they seek to remedy in the large
number of patients they see every day. Emergency, trauma, and acute conditions get
precedence over chronic conditions in allocating medical manpower (Bergen, 2013). The
patient-physician ratio of 1 doctor for 2,000 patients admitted by the Indian Government

11
is deficient for providing acceptable-quality healthcare. The modern medicine healthcare
system in India does not have the requisite manpower and medical professionals to
address a problem of this scale and magnitude.
India also has a matching number of practitioners of AYUSH. I have researched
the premise that if traditional and modern systems of medicine joined forces to address
the emerging diabetes pandemic, there could be a significant improvement in health
outcomes. According to the Department of AYUSH, there are 750,000 practitioners of
AYUSH in the country (Appendix D). With the support of traditional medical
professionals of AYUSH, the manpower available to tackle the problem of diabetes more
than doubles, and the goal becomes more achievable. Presently, both the modern and
traditional schools of medicine work independently of each other, but with their joint and
collaborative skills, the patient community could greatly benefit.
The challenge posed by diabetes in India needs synergistic effort and a
compassionate and cohesive integrative approach. With 600,000 practitioners of modern
medicine and a matching, if not larger, number of practitioners of traditional medicine
who serve a population of 1.2 billion people, India is ill equipped to provide adequate and
basic healthcare to its people (Appendices D & E). India needs a composite and
integrated healthcare approach. Through this case study, I explored the possibility and
feasibility of a unified and integrative strategy that combines the skills and outreach of
traditional and modern medicine to address the emerging diabetes pandemic in India.
Purpose of the Study
The purpose of this study was to assess the practicability of using an integrative

12
approach as a potential solution for India’s emerging diabetes pandemic. The case for the
study was the emerging pandemic of diabetes in India and the possibility of using an
integrative approach to meet the challenge posed by the emerging pandemic of diabetes.
The scale and enormity of the task posed by diabetes in India possibly warrants an
integrative and complementary role for modern and traditional systems of medicine like
AYUSH. The case study approach was most appropriate for the study of the emerging
diabetes pandemic in India. Yin (2009) describes case study as “an empirical enquiry
about a contemporary phenomenon set within its real-world context—especially when the
boundaries between phenomenon and context are not clearly evident” (p. 18).
The proposed solution investigated in the case study involved a collaborative and
integrative role for the modern and traditional systems of medicine in addressing the
challenge of diabetes in India. The traditional systems of medicine are widely accessed in
India and offer both an economical and an alternative solution (Public Broadcasting
Service, 2011). Through this study, I investigated the rationale and desirability of using
an integrative approach to address the emerging diabetes pandemic in India. The study
was an effort to fill a significant existing gap in scholarly literature on the subject of
using an integrative approach to address diabetes. The findings of the study could
potentially add value and significance to knowledge for the containment of diabetes in
India.
Research Questions
The two research questions addressed in this dissertation were the following:
1. How can the modern and traditional medicine approaches be jointly deployed

13
to contain the spread, scale, and immensity of the emerging diabetes pandemic
in India?
2. What are the challenges and barriers of combining the methodologies
propounded by traditional systems (AYUSH) with those of modern medicine
in containing diabetes?
The purpose of this study was to assess the practicability of using an integrative
approach as a potential solution for India’s emerging diabetes pandemic. With this
purpose, I also used interviews to obtain information on strategies for containment of
diabetes from all major traditions of medicine practiced in India. The interview process
included both the modern medicine and traditional medicine streams. The objective, as
stated above, was to combine the researched findings of interviews with traditional and
modern systems to explore the possibility of a unified, complementary, and integrative
approach to the containment and management of diabetes. The explanatory questions of
what and how are best answered using the case study approach.
Nature of Study
Theoretical Framework
The above-stated research questions were studied using the qualitative research
methodology. The qualitative research design was the most appropriate for answering the
research questions of this nature because an understanding of community psyche was
essential to explore the subject of study in the dissertation. Quantitative and mixed
methods would not have been as appropriate because this study was not just about cold
numbers and trends analysis but was an in-depth analysis of the new possibilities to arrest

14
the emerging pandemic growth of diabetes in India.
As this research was conducted in an attempt to generate an action agenda, the
involvement of healthcare providers and policy makers as key stakeholders was essential.
The most appropriate theoretical framework selected to address the phenomenon of
diabetes was participatory action research, as the research involved the participation of all
stakeholders. McCutcheon and Jurg (1990) posited that action research is systematic
inquiry that is collective, collaborative, self-reflective, and critical and that is undertaken
by the participants (McCutcheon & Jurg, 1990). The research involved intensive
interaction with practitioners of modern medicine and practitioners of traditional systems
AYUSH to obtain the requisite information; thus, the nature of the study made it
appropriate for the participatory action research framework. In this study, I investigated
whether collaboration and interaction between practitioners of different systems will
enhance and improve the knowledge of all involved as well as lead to actions of change
and provide concrete solutions to the prevention and treatment of diabetes.
Diabetes is both a social and a medical phenomenon (Oregon Strategic Plan,
2008). To understand the issue of diabetes in India, I used the case study research
approach. “Case study research involves the study of an issue explored through one or
more cases within a bounded system,” (Creswell, 2007, p. 73). A unique situation exists
in India, as it is home to several indigenous and indigenized foreign systems of medicine.
It is necessary to address and arrest the growing incidence of diabetes in this country. All
case study research starts with the same compelling feature: the desire to derive an in-
depth understanding of a single or small number of “cases,” set in their real-world

15
contexts (Bromley, 1986, p. 1). The solution of the case examined in this study was the
feasibility and challenges of deploying an integrative approach to address the challenge
posed by India’s emerging diabetes pandemic. The constituent systems of AYUSH and
modern medicine were the key components of the participatory action research design.
The tools for data collection in this study were observation, interviews, and
review of available research and policy documents. Observation and interview form the
basis of qualitative research (Creswell, 2007). Detailed interaction with medical
practitioners of different traditions helped in generating the requisite information and data
for analysis of the research questions. The process of interviews constitutes the core of
qualitative methodology (Creswell, 2007). This research involved analysis of information
and data from medical practitioners (both modern medicine and traditional AYUSH
practitioners). An in-depth investigation into guidance of process, diet, and lifestyle for
averting chronic noncommunicable diseases such as diabetes was best addressed using
qualitative methods of investigation. I conducted interviews with a select group of
medical practitioners from different schools and traditions of medicine, as well as policy
experts. The collaborative efforts, skills, and experiences of the medical practitioners
enriched the body of information regarding the possible role of an integrative approach to
managing diabetes. It also emerged that collaborative and innovative integrative
processes could be effectively used for the detection, prevention, and management of
diabetes. The collaborative and inclusive approach emerging out of the process of
participatory action research helped to establish a case for usage of an integrative

16
approach combining modern medicine methods and traditional Indian medicine methods
to prevent and contain diabetes.
Research Methodology
The qualitative data for this study came from three sources.
1. A search of scholarly literature and policy documents on diabetes in modern
medicine and in traditional medical systems (AYUSH).
2. Structured interviews with 30 medical practitioners: five physicians from
modern medicine and five medical practitioners from each of the AYUSH
traditions: Ayurveda, yoga and naturopathy, unani, siddha, and homeopathy.
3. Structured interviews with six public health policy planners and health
administrators.
The 36 interview responses provided the data saturation necessary to obtain
answers to the research questions. The interviews were conducted after obtaining all
required permissions and approvals. Interviews were recorded when so allowed and
transcribed using appropriate tools and software to create a comprehensive information
base. The qualitative data collected from observations and interviews were analyzed to
find answers to all the research questions. The analyzed data were also used to create a
summary of methods for containment of diabetes propounded by the modern and
traditional schools of medicine.
Definitions
The definitions of various terms used in this dissertation are provided below.
AYUSH is the acronym used by the Government of India to refer collectively to the major

17
streams of traditional medicine practiced in India. The acronym AYUSH expands into
Ayurveda, yoga-naturopathy, unani, siddha, and homeopathy. Very recently, Sowa-Rigpa
was added to the purview of AYUSH.
Ayurveda: Literally means “the art and science of living.” Life in Ayurveda is
conceived as the union of body, senses, mind and soul. The living man is a
conglomeration of three humors (Vata, Pitta, and Kapha—air, fire, and water); seven
basic tissues (Rasa—juice, Rakta—blood, Mansa—flesh, Meda—plasma, Asthi—bone,
Majja—tissue, and Shukra—semen); and the waste products of the body such as feces,
urine, and sweat. Thus, the total body matrix consists of the humors, the tissues, and the
waste products of the body. The growth and decay of this body matrix and its constituents
revolve around food, which gets processed into humors, tissues, and wastes. Ingestion,
digestion, absorption, assimilation, and metabolism of food have interplay in health and
disease, which is significantly affected by psychological mechanisms as well as by bio-
fire (Agni); (Ministry of Health and Family Welfare, India, 2011).
Gestational diabetes mellitus (GDM): Glucose intolerance with onset or first
recognition during pregnancy. GDM affects at least 1 in 25 pregnancies globally.
Undiagnosed or inadequately treated GDM can lead to larger than normal babies and
higher rates of maternal and infant deaths and fetal abnormalities. Women with GDM and
the offspring of GDM pregnancies are at increased risk of developing Type 2 diabetes
(IDF, 2011). The three types of diabetes are depicted in the figure on the next page,
which also highlights the fact that nearly 46% of people with Type 2 diabetes remain
unaware of the reality of their medical condition.

18
HbA1c: Refers to the glycated or glycosylated hemoglobin test, which is an
accepted gold standard pathological measure of average levels of blood sugar over a 90-
day period. Glucose in the bloodstream sticks to the red cells hemoglobin to make a
“glycosylated hemoglobin” molecule, called hemoglobin A1c or HbA1c. The more
glucose in the blood, the more hemoglobin A1c or HbA1c will be present in the blood.
Red cells live for 8-12 weeks before they are replaced. Measuring the HbA1c reveals the
increase in blood glucose levels over a period of 8-12 weeks. A normal nondiabetic
HbA1c is 3.5-5.7%. This is used as a confirmatory test to establish the presence or
absence of diabetes in patients (ADA, 2012). The pathology and physiology of HbA1c
are explained in the IDF diagram below, whereby the measure is able to capture the
average blood glucose content for the 90-day period.
Homeopathy: The word homoeopathy is derived from two Greek words, homois
meaning “similar” and pathos meaning “suffering.” Homoeopathy simply means treating
diseases with remedies, prescribed in minute doses, which are capable of producing
symptoms similar to the disease when taken by healthy people. It is based on the natural
law of healing—Similia Similibus Curantur, which means “likes are cured by likes.” It
was given a scientific basis by Dr. Samuel Hahnemann (1755-1843) in the early 19th
century (Ministry of Health and Family Welfare, India, 2011).
Integrative: Refers to a medical approach that combines best practices and
learnings from multiple medical traditions. In the context of this study, integrative
approach refers to an approach that seeks to combine modern medicine with traditional
schools of medicine (AYUSH).

19
Naturopathy: A system of living in harmony with the constructive principles of
nature on physical, mental, moral, and spiritual planes of living. It has great health-
promoting, disease-preventive, curative, and restorative potential. According to the
manifesto of the British Naturopathic Association, "Naturopathy is a system of treatment
which recognizes the existence of the vital curative force within the body." It therefore
advocates aiding the human system to remove the cause of disease (i.e., toxins) by
expelling the unwanted and unused matters from human body for curing diseases
(Ministry of Health and Family Welfare, India, 2011).
Siddha: Describes the human body as a replica of the universe, as are food and
drugs, irrespective of their origin. Like Ayurveda, this system involves the belief that all
objects in the universe, including the human body, are composed of five basic elements:
earth, water, fire, air, and sky. The food that the human body takes and the drugs it uses
are all made of these five elements. The proportions of the elements present in the drugs
vary, and their preponderance or otherwise is responsible for certain actions and
therapeutic results (Ministry of Health and Family Welfare, India, 2011).
Sowa-Rigpa: This system of medicine is based on the principles of Jung-wa-nga
(five elements) and Ngepa-Sum (three flaws of the body). Bodies of all the living beings
and nonliving objects of the universe are composed of Jung-wa-nga; Sa, Chu, Me, Lung,
and Nam-kha (earth, water, fire, wind and ether). The physiology, pathology,
pharmacology, and metria-medica of this system are established on these theories. The
human body is composed of these five cosmo physical elements of Jung-wa-nga; when
the proportion of these elements is in imbalance in the body, disorder results. The

20
medicine and diet used for the treatment of disorders are also composed of the same five
basic elements. In the body, these elements are present in the form of Ngepa-Sum (Tri-
dosa) Lus-sung-dun (Sapta Dhatu), and Dri-ma-Sum (Ministry of Health and Family
Welfare, India, 2011). Sowa-Rigpa equates good health with a high level of energy and
recognizes diet, behavior, and forms of medicine and external intervention as its pillars.
This approach is consistent with the philosophy of other AYUSH traditions.
etan
Figure 4. Tibetan health system. From presentation at the Congress of Traditional Asian
Medicine, by T. Kalsang, 2013, Dharamsala, India.
Type 1 diabetes: An autoimmune disease that destroys the insulin-producing cells
of the pancreas. It accounts for 3-5% of all diabetes globally. It most commonly develops
in children and young adults but can occur at any age. People with Type 1 diabetes are
always dependent on insulin injections or pumps for survival. There is as yet no proven
widely available therapy to prevent or cure Type 1 diabetes (IDF, 2011).
Balancing Energies through Four modes of
Treatment
D
A
B
A
F of
M
E Therapy
• D approach
• C Intake
• D Restrictions
• R
B
• I
B
• S
B
• D
• P
• P
• M paste
• M butter
• M ash
• C decoction
• M wine
• G medicines
• H compounds.
M
T
• H or cold
• M
• M -hot
•
bath
• V
• C
• M
• G -
• S is
only a
resort.
D
T

21
Type 2 diabetes: Occurs due to a combination of insulin resistance and insulin
deficiency. It accounts for 95% or more of all diabetes globally. It most commonly occurs
in middle-aged and older people but increasingly affects overweight children,
adolescents, and young adults. It is particularly affecting people in the productive years
of the life cycle. People with Type 2 diabetes are usually treated with oral medication.
Many also require insulin injections, depending upon the extent of disease in the body. It
can be prevented or significantly delayed by simple and cost-effective interventions.
There is no known permanent cure for Type 2 diabetes as of now (IDF, 2011).
Figure 5. Three types of diabetes. From Global Diabetes Atlas (6th ed.), by the
International Diabetes Federation, 2013. Retrieved from http://www.idf.org/sites/default
/files/ The_Global_Burden.pdf
Unani: A system of medicine based on the underlying science of Tibb. This system
describes the various states of body, in health and when not in health, and the means by
which health is likely to be lost and, when lost, is likely to be restored. The Unani system

22
is based upon the four-humor theory of Hippocrates. This presupposes the presence of
four humors in the body: blood, phlegm, yellow bile, and black bile. The Unani system
considers the human body to be made up of the following seven components: Arkan
(elements), Mizaj (temperament), Akhlat (humors), Aaza (organs), Arwah (spirits), Quwa
(faculties), and Afaal (functions). (Ministry of Health and Family Welfare, India, 2011).
Yoga: A discipline to improve or develop one’s inherent power in a balanced
manner. It offers the means to attain complete self-realization. The literal meaning of the
Sanskrit word yoga is “yoke.” Yoga can therefore be defined as a means of uniting the
individual spirit with the universal spirit of God. According to Sage Patanjali (believed to
be the first proponent of yoga), yoga is the harnessing of modifications of the mind to
create a harmony and union of body, mind, and spirit. Yoga and yogic processes have
been used as an effective medium for prevention of disease and treatment of certain kinds
of diseases.
Assumptions
In this study, I made three principal assumptions. The first assumption was that
the urgency to address the emerging diabetes pandemic in India was widely shared by
policy planners and medical professionals. The second assumption was that among the
key stakeholders, there was a desire and openness to look at new and different
approaches to successfully addressing the challenge posed by the emerging diabetes
pandemic. The third assumption was that there was candidness on part of practitioners of
both streams of medicine, modern and traditional, to consider the hypothesis that it may
be possible to work together for the larger good of the community and that an integrative

23
approach might be feasible and practical to achieve certain predefined results or
expectations. During the course of interviews and analysis of data, all three assumptions
were fully validated.
Limitations
The primary limitation of this study was that the conclusions were drawn from
interaction and interviews with a relatively small participant pool of 30 medical
professionals and six policy planners. Small sample size is an inherent limitation of the
qualitative research methodology. As the sole interviewer and data analyst, my bias could
have been, in theory, a limiting factor. The third limitation of the study was that it
excluded the newest member of AYUSH, Sowa-Rigpa, as enough information on this
stream of AYUSH was not yet available. During the process of literature review, I also
found that guiding principles of Sowa-Rigpa were similar to Ayurveda, and I have
brought this out in later chapters of this study. To the best of my knowledge and belief,
none of the three limitations impacted the robustness of the process of research and
analysis and/or conclusions of the study.
Scope and Delimitations
In the study, I focused on the key influencers of diabetes—namely, medical
professionals and the policy planners. Though the sample size was small, the key
perceptions of the participants were convincingly captured through interviews and
observation to generate rich data to draw appropriate conclusions. The key delimitation
strategy was to vigilantly abstain from any form of bias. To enlist participation of
physicians and policy planners, I sought their informed consent prior to conducting the

24
interviews. The case study approach helped to create the building blocks for a larger
consensus on the benefits of this approach.
Significance of the Study
The significance of this study lay in proposing a case for using an integrative
approach to address the phenomenon of diabetes in present-day India. The case study
became an inquiry to understand the phenomenon and challenges of the emerging
diabetes pandemic in India. The purpose of this study was to assess the practicability of
using an integrative approach as a potential solution for India’s emerging diabetes
pandemic.
The findings from this research study have the potential to make meaningful
contributions both to the body of knowledge and to its application. Research should
contain an action agenda for reform and change (Creswell, 2007). The significance of this
study was in its potential to initiate action and change. During the course of research, I
realized that the proposed joint participation of healthcare practitioners and policy makers
had resulted in a useful dialog between and among the key stakeholders. By evaluating
the feasibility and practicability of co-engagement of the modern and traditional streams
of medicine, this study created the potential to initiate a synergistic approach between and
among various schools and traditions of medicine for the greater wellbeing of the patient
population. This study resulted in enrichment of knowledge in the area of collaborative
and integrative medicine. The literature search during the period of this study did not
bring out any scholarly papers whose authors had studied or recommended an integrative
approach as a possible solution for the containment of diabetes in India or the world.

25
In its 10-year Global Diabetes Plan for the period 2011-2021, IDF opened the
discussion on improving health outcomes of people with diabetes with the following
statement: “Diabetes causes immeasurable personal suffering and costs to society and
slows human and economic development. Complications are not inevitable. We know
what to do—the time to act is now” (IDF, 2011, p. 10). In the same document, IDF
identified three outcomes that could be used to measure the success of any diabetes-
related initiatives. Per IDF (2011), the first desirable outcome of any such initiative
should be that people with diabetes should have greater access to essential medicines,
technologies, and help. The second desirable outcome is that the initiative should benefit
people with impaired glucose intolerance who run the risk of becoming diabetic.
The third desirable outcome identified by IDF is that all comorbidities in people
with diabetes are properly diagnosed and treated. The conclusions of this study have
successfully contributed to all the three identified outcomes. The first contribution was
that it successfully added to the body of knowledge regarding control and management of
diabetes by drawing attention to tips and solutions from other medical traditions. The
proposed collaborative framework of modern and traditional streams of medicine
championed by this study may lead to the availability of a larger pool of medical
resources to diagnose and treat the patient population. The increased access to the joint
medical pool might eventually help all three types of people—people with prediabetes
symptoms, people with diabetes, and people with comorbidities of diabetes.
The conclusions of the study sow the seeds for initiating positive social change.
First, the study created a body of information, which, if implemented, can increase

26
medical touch points for patients. Medical practitioners of different traditions, according
to the interviews and findings, may be able to communicate key preventative measures
regarding diabetes to the patients they see. Second, the study created the potential to
successfully draw the attention of policy administrators to align and fine-tune policy
initiatives that may result in wider and beneficial implications for a society that is battling
the scourge of diabetes. Third, the study may help stakeholders to suggest integrative,
wholesome and affordable approaches to preventing the incidence of diabetes and
possibly other forms of noncommunicable disease in the future.
The social change factors of this study will arise from the acceptance of
traditional medicine by people, practitioners, policy makers, and society at large. The
more inclusive medical engagement of various traditions might receive wider support
both from the state and the society. This study compiles basic information on prevention
and management of diabetes from both streams of physicians (modern and traditional
medicine) and public health policy administrators. The study adds to the body of
knowledge and initiates the process of further research. The study may lead to positive
social change, both in the public health scenario and in the lives of individuals and
communities. Collaborative efforts in the future might lead to joint clinical trials to
validate the efficacy of traditional methods and medicines, which, in turn, may inspire
greater confidence in their usage and ensure better quality of products and services that
will benefit the patient community in India and the world.
This research has the potential of causing positive social change in the lives of
people by highlighting well-researched modes of diet and lifestyle changes as

27
championed by various medical traditions (Hu, Wallace, & Tesh, 2010). Innovative ways
of prevention and containment of diabetes will save valuable socioeconomic resources in
the large developing economy of India (Shetty, 2012). IDF (2011) is of the view that
diabetes is not only a health crisis, but also a global societal catastrophe. Governments
worldwide are struggling to meet the cost of diabetes care. Costs to employers and
national economies are escalating, and every day, low-income families are being driven
into poverty by loss of earnings due to diabetes and the lifelong costs of healthcare (IDF,
2011).
Summary
The findings of this study may lead the medical research councils of all traditions
of medicine to issue an advisory that medical practitioners should take a few moments to
talk about the risk factors of diabetes to all patients. This is a powerful recommendation
that arose from the interview process. WHO (2010) has reported that India has 15% of
the world’s population and carries 20% of the global burden of diseases. Diabetes forms a
significant component of this burden. Diabetes also leads to other degenerative health
conditions. India’s pool of 600,000 practicing doctors from the modern medicine stream
is inadequate to meet the health needs of 1.2 billion people. A large number of Indians
access health services provided by a similar number (750,000) of AYUSH practitioners
in the country. The two work independently of each other. India’s annual spending on
management of diabetes is less than USD 5 billion (Ministry of Health and Family
Welfare, 2011). The projection of diabetes as a ticking time bomb is a grim but true
description (Shetty, 2012).

28
In this study, the possibility of combining the outreach of both the modern and
traditional streams of medicine to contain an emerging pandemic of diabetes was
explored. The qualitative research of this study established the feasibility of this
proposition and looked at challenges as well as solutions that could make this process
work for the larger good of the country and its health needs. The joint efforts of medical
practitioners of various streams and policy makers, as inspired by this study, may lead to
the action of change as suggested in the framework of participatory action research.
By maximizing the possibilities of timely detection and treatment of diabetes, the
findings of this study may also help many people with diabetes avoid the comorbidities
and health complications that follow untreated diabetes in tow.

29
Chapter 2: Literature Review
Introduction
The purpose of this study was to assess the practicability of using an integrative
approach as a potential solution for India’s emerging diabetes pandemic. Diabetes is
acknowledged as a formidable public health challenge both in India and the rest of the
world. The increased prevalence and the current methods of prevention are unable to
contain the rate of growth among the large numbers of people with impaired glucose
intolerance (prediabetics). The impact of diabetes is felt globally. Both developing and
developed countries are struggling to come to terms with the many dimensions of this
disease. The top 10 countries with diabetic populations include both developing and
developed nations, as can be seen in the figure below. Three of world’s richest
countries—namely, the United States, Japan, and Germany—also appear in the list of the
top 10 nations with diabetic people, together with highly populated countries such as
China, India, and Indonesia.
Figure 6. People with diabetes: Top 10 countries. From Global Diabetes Atlas (6th ed.),
by the International Diabetes Federation, 2013. Retrieved from
http://www.idf.org/sites/default /files/ The_Global_Burden.pdf

30
The literature reviewed revealed the magnitude of the problem created by the
continuing rapid growth of diabetes. Diabetes has been described as a pandemic or a
ticking time bomb by researchers, authors, and scholars. The stated position of IDF
(2011) is that 95% of the total incidence of diabetes is both preventable and avoidable.
The purpose of this study was to examine the feasibility, desirability, and challenges of
combining the methods and outreach of modern medicine and traditional medicine to
address the emerging pandemic of diabetes in India. Diabetes is a challenge not just for
India, but also for the entire world.
Data provided by the American Diabetes Association (ADA; 2013) and the
World Health Organization (WHO, 2010) reveal that approximately 24.4 million or
11.3% of the U.S. population over the age of 20 years has diabetes—diagnosed or
undiagnosed. The economic cost of managing diabetes in the United States in the year
2013 was USD 245 billion (ADA, 2013). While this might be less than 10% of U.S.
annual health spending, it sets a context for the magnitude of the challenge in developing
countries such as India. India’s total healthcare spending is USD 65 billion, and its
diabetic population is 2.5 times larger than that of the United States (IDF, 2013). The IDF
(2011) has categorically stated, “Diabetes is at crisis levels. We cannot afford to delay
action any longer; the human misery and suffering caused by diabetes is unacceptable
and unsustainable” (p. 1).
The IDF (2011) has reported that there is compelling evidence in both developed
and developing countries to suggest that both diabetes and complications of diabetes can
be successfully addressed with timely and proper screening, diagnosis, and treatment

31
(IDF, 2011). The evidence in the reviewed scholarly literature reinforces the importance
of timely medical intervention and guidance. In countries or situations where this
possibility is delayed or denied to all or a section of people, the situation has resulted in
an increasing number of people with diabetes. Alam, Speed, and Beaver (2012) examined
the status of diabetic British nationals of Bangladeshi descent living in the United
Kingdom and found that the Bangladeshi community possibly experienced some of the
weakest diabetes-related health outcomes in the United Kingdom.
Alam et al. (2012) found that not much was known about the experiences and
preferences of British Bangladeshi settlers in accessing locally available diabetes
healthcare information and services. The group of people studied by Alam et al. did not
benefit from the available services or even have awareness of the existence of those
services in the United Kingdom. The conclusions reached by Alam et al. related to four
popular domains of health access: availability of health services, use of health services,
outcomes of health services, and perception of equity by the patient population. All of
these domains are important to make a visible difference to verify the success of remedies
to beneficially influence the pace of growth of diabetes.
The literature search strategy used for reviewing scholarly literature is discussed
in detail later in this chapter. This is followed by explanation of theoretical foundations
used in the dissertation. The theoretical foundation dovetails into a review of the
conceptual framework that was used in my research. This is followed by a review of
scholarly literature related to key variables and concepts before the chapter concludes
with a summary of key points.

32
Literature Review Strategy
The literature search was done on major medical and health search engines
including PubMed, EBSCO, High Wire Press, ProQuest Health, Sage, MEDLINE and
Cumulative Index to Nursing and Allied Health (CINAHL). The strings that were
searched were diabetes, diabetes pandemic, diabetes research, diabetes lifecycle,
diabetes challenges, diabetes in India, diabetes in developing world, alternative ways of
addressing diabetes, traditional medicine and diabetes, Ayurveda and diabetes, yoga and
diabetes, Siddha and diabetes, Unani and diabetes, homeopathy and diabetes,
naturopathy and diabetes, Rigpa and diabetes, modern and traditional medicine and
diabetes, phenomenological approach in medicine/health research, and participatory
action research in medicine/health. The 108 research papers that were selected after the
search process were carefully reviewed. A wide cross-section of the reviewed papers has
been presented in terms of their points of connection and differences with the theme of
this dissertation.
The reviewed literature was from all parts of the world and covered a wide gamut
of issues related to the disease and its medical, preventive, and educational dimensions. It
was found that while the research community had studied a large number of problems
related to diabetes globally, it had not yet studied or commented upon the possibility of
combining the outreach and capacity of modern and traditional systems of medicine to
combat diabetes. The possibilities of using an integrative approach combining modern
and traditional medicines had not yet been addressed in the literature available in print
and electronically. That made the subject of research of this dissertation of topical interest

33
and relevant, given the gravity of the challenge posed by diabetes in India and the rest of
the world.
Theoretical Foundation
Health and medical researchers explore a wide range of scholarly pursuits and use
various types of theoretical frameworks for research design. The success of research lies
in using the most appropriate theoretical framework relevant to the problem and scope of
research. Depending upon the problem being researched, researchers may seek to derive
their concepts from Maslow’s humanism and social hierarchy, Durkheim’s functionalism,
Weber’s empiricism, Lewin’s participatory action, Merton’s goal-means gap theory,
Kuhn’s symbolic interactionism, Bandura’s social cognitive research, or Garfinkel’s
ethnomethodology (Franzoi, 2006).
The theoretical foundation selected for this study was participatory action
research. Participatory action research (PAR) is the theory of choice for research that
involves community residents, key influencers, clients, and other constituents in research
plans that are intended to lead to social change (Kemmis, 1980). It is used when
participants work with an anchor or a research facilitator to identify a common problem,
develop research methodology, collect data, and analyze findings. In participatory action
research, the data collected provide valuable cues to the researchers, and the data are
often used to design recommendations as to how the problem should be addressed,
analyzed, and resolved. In many situations involving participatory research, the
participants lobby for or support a case for funding, legislation, or government action to
adopt and publicize the findings. Participatory action research maximizes the likelihood

34
that the resulting program or intervention will meet the broader needs of key stakeholders
and be appropriate for the prevailing conditions and environment, leading to action and
change.
The rationale for participatory action research finds support in the powerful
concept of paradigm introduced by Kuhn (1996). Kuhn defined paradigm as a
combination of two characteristics— the phenomenon (a) is attractive enough to engage
peer attention and (b) is open enough to “assimilate enrichments and improvements”
(Kuhn, 1996, e-location 285 of 3697). Referring to the development of science, Kuhn
said that transitions from one paradigm to another via revolution lead to mature science.
Kuhn conceded that reaching or attaining consensus in science can be difficult or even
illusive. He also contended that no scientific concept can possibly answer all questions or
explain all facts. Kuhn saw an interactive integrative process at work in science. A single
problem or scientific theme is viewed and addressed differently by different branches of
science (Kuhn, 1996). Kuhn further elaborated on the distinction between the process at
work while solving problems and the process at work in creating something completely
new.
Kuhn argued that discovery starts with awareness of an anomaly. He defined an
anomaly as a situation in which a paradigm-induced expectation has been violated (Kuhn,
1996). Kuhn (1996) also reminded the reader that scientific discoveries and inventions
are often greeted with suspicion and skepticism. He cited the example of the discovery of
X-rays, which was treated by fellow scientists as a “hoax” (Kuhn, 1996, e-location 983 of
3697). Kuhn said that, in science, innovation emerges only with much effort and against

35
stiff resistance (Kuhn, 1996). Kuhn considered all scientific discoveries to be the result of
a “paradigm change” (Kuhn, 1996, e-location 1057 of 3697). Crisis, said Kuhn, is a
necessary precursor to innovative theories and development, which need to be useful for
the society and community. In this study, I used the participatory action research theory
to draw attention to the crisis of diabetes to initiate action for change in the healthcare
system.
Lewin, who coined the term action research, stated,
The research needed for social practice can best be characterized as research for
social management or social engineering. It is a type of action research, a
comparative research on the conditions and the effects of various forms of social
action, and research leading to social action. Research that produces nothing but
books will not survive. (Lewin, 1946, reproduced in Lewin 1948, pp. 202-203,
Laureate Tutorial)
Jane Addams, the first female Nobel Prize winner, used her data collection methodology
regarding social conditions to bring about social change. Her writings revealed the true
usage of action research that leads to social change (Laureate Tutorial). In this study, I
used participatory action research to explore the possibility of adapting an integrative
approach combining modern and traditional methods of medicine to address the
phenomenon of diabetes.
The use of the participatory action research framework helped me initiate active
involvement and discussion within the community of medical practitioners and
policymakers to find innovative ways of preventing and containing diabetes. The process

36
of interviews and discussions with medical practitioners brought out the need for medical
consultations and intervention to become more patient oriented. Theorist Stringer, in
explaining participatory action research, referred to the acquisition/production of
knowledge as a collective process. This process, posited Stringer (2007), engages people
who have previously been the subjects of research in the process of defining and
redefining the study and the corpus of understanding. Stringer also stated that the stakes
of participants are high if the subject of research relates to participants’ community or
organizational life. As people collectively analyze and investigate their own situation,
stakeholders end up building a consensual vision of their life-world. “Community-based
action research results not only in a collective vision but also in a sense of community. It
operates at the intellectual level as well as at social, cultural, political, and emotional
levels” (Stringer, 2007, p. 11).
Lewin is often considered the harbinger of the idea of participatory action research
(PAR). In the book Strategies of Qualitative Inquiry and in a paper presented to the
Annual Meeting of the Australian Association for Research in Education (Sydney,
Australia, November 6-9, 1980), Kemmis described participatory action research as a
theory that began with an “idea” attributed to social psychologist Lewin (1980). Lewin
introduced this idea in the Tavistock Institute of Human Relations in the United Kingdom
in 1933 and again in 1936. Lewin used the term to describe a form of research that could
marry the experimental approach of social science with programs of social action in
response to major social problems of the day. Through action research, Lewin argued,
advances in theory and needed social change might simultaneously be achieved (Kemmis

37
& McTaggart, 1988).
Authors who have cited Lewin consider action research as consisting of analysis,
fact-finding, conceptualization, planning, execution, and more fact-finding or evaluation
(Kemmis & McTaggart, 1988). Kemmis & McTaggart (1988) restated that PAR,
according to Lewin, entails planning a change, acting and observing the process and
consequences of the change, reflecting on these processes and consequences, replanning,
acting and observing again, and reflecting again. Collaboration is the key in PAR. The
subjects of participatory action research undertake their research as a social practice. The
object of participatory action research is social. Participatory action research is directed
toward studying, reframing, and reconstructing social practices. Practices are constituted
by social interaction between people.
Changing practices is a social process and has long-term consequences. Social
change is initiated when one person changes so that others are obliged to react or respond
differently to that individual’s changed behavior. The willing and committed involvement
of other segments of society is necessary to secure and legitimize the change.
Participatory action research offers an opportunity to create forums in which people can
join one another as coparticipants in the struggle to remake the practices in which they
interact—forums in which rationality and democracy can be pursued together without an
artificial separation (Kemmis & McTaggart, 1988).
Habermas (1984) described this process in terms of opening communicative space
in his book Theory of Communicative Action. Participatory action research is a social
process of collaborative learning realized by groups of people who join together in

38
changing the practices through which they interact in a shared social world in which they
are impacted and influenced by each other’s actions. Participatory action research
involves the investigation of actual practices and not abstract practices. It involves
learning about the real, material, concrete, and particular practices of particular people in
particular places. Participatory action research differs from other forms of research in
being more determined on changing practitioners’ particular practices. Participatory
action researchers may be interested in practices in general or in the abstract, but their
principal concern is in changing practices (Denzin & Lincoln, 2007).
Senge and Scharmer (2006), in their essay on participative research, also praised
the many benefits of using this approach in social science research where the desire is for
wider community agreement. Senge separately also alluded to the benefits of
participative research in situations where intense subject engagement is involved in his
well-known book The Fifth Discipline (1990). The design for this study essentially
sought to serve the larger good of the community through optimal use of scarce medical
resources available in India. There are three weaknesses in the current medical system of
India for optimal treatment of diabetes. First, there are insufficient medical professionals
from the modern medicine domain to address the emerging pandemic of diabetes.
Second, the available medical resources are not deployed optimally in a strategic manner
for the management of disease. Third, no efforts have been made to combine the outreach
of modern medicine stream with the traditional medicine stream to address the health
problems of the India (Shetty, 2012).
Participatory action research is the method of choice when there is active and

39
interactive involvement of community residents and stakeholders in research oriented for
social change. In participatory action research, the data are often used, as stated earlier, to
make recommendations and policy corrections as to how the problem should be
addressed and resolved. In the PAR mode of research, participants are also known to
lobby for funding, legislation, or government action to adopt the findings. Participatory
action research maximizes the likelihood that a resulting program or intervention will
meet the needs of stakeholders and be culturally appropriate, using the four-step cycle
created by Lewin (plan, act, observe, and reflect). Participatory action research is an
ongoing process where stages of observing, planning, taking action, and evaluating the
process that is taking place through reflection are recurring to bring about social change.
The underlying objective of participatory action research is to bring social change
through stakeholder engagement.
Participatory Action Research in Health Sciences
PAR has been used in health sciences research as a forerunner for social change.
Researchers Carey and Smith, in their 1992 study, used a combination of qualitative and
participative methods to design a research program to understand the phenomenon of
HIV in their community. Carey and Smith (1992) evaluated a number of alternatives
before selecting the participative method. Carey & Smith (1992) concluded that the
participatory action research methods were of value in designing the program that would
make the HIV research in their community more meaningful and impactful.
In the study by Brown et al., (2008) on urban health disparities participatory
action research, the authors demonstrated the benefit of involving stakeholders in the

40
development of the hypothesis and its explanation. Khan, Vinayagam, Sekar, Palanivelu
& Panchanandham (2012) used the participatory action research premise to demonstrate
the antidiabetic and antioxidant effect of Semecarpus anacardium (nut milk extract) in a
rat model. In another study, Gardner et al. (2011) used the participatory action research as
the methodology to establish the beneficial effects of an innovative quality improvement
process in remote parts of Australia and South Pacific.
Conceptual Framework
The purpose of this study was to assess the practicability of using an integrative
approach as a potential solution for India’s emerging diabetes pandemic. Diabetes is a
phenomenon of grave consequences both for an individual and the community and a
gigantic public health challenge. The intent of this study was to connect all the available
medical professionals, modern and traditional, in the country’s mainstream health system
to enhance the outreach of medical services to people and improve health outcomes of
diabetes. The underlying assumption was that the enhanced medical outreach would lead
to more timely detection of diabetes and will either prevent its occurrence or help people
manage the consequences of disease in a better manner. As a researcher, I explored the
research questions using the participatory action research principles. I conducted
intensive qualitative interviews with major stakeholders who had the influence and ability
to initiate change in methods to address the challenge of diabetes.
The participatory action research ought to have a conceptual framework.
(Coghlan, & Brannick, 2005). The conceptual framework used in this study is explained
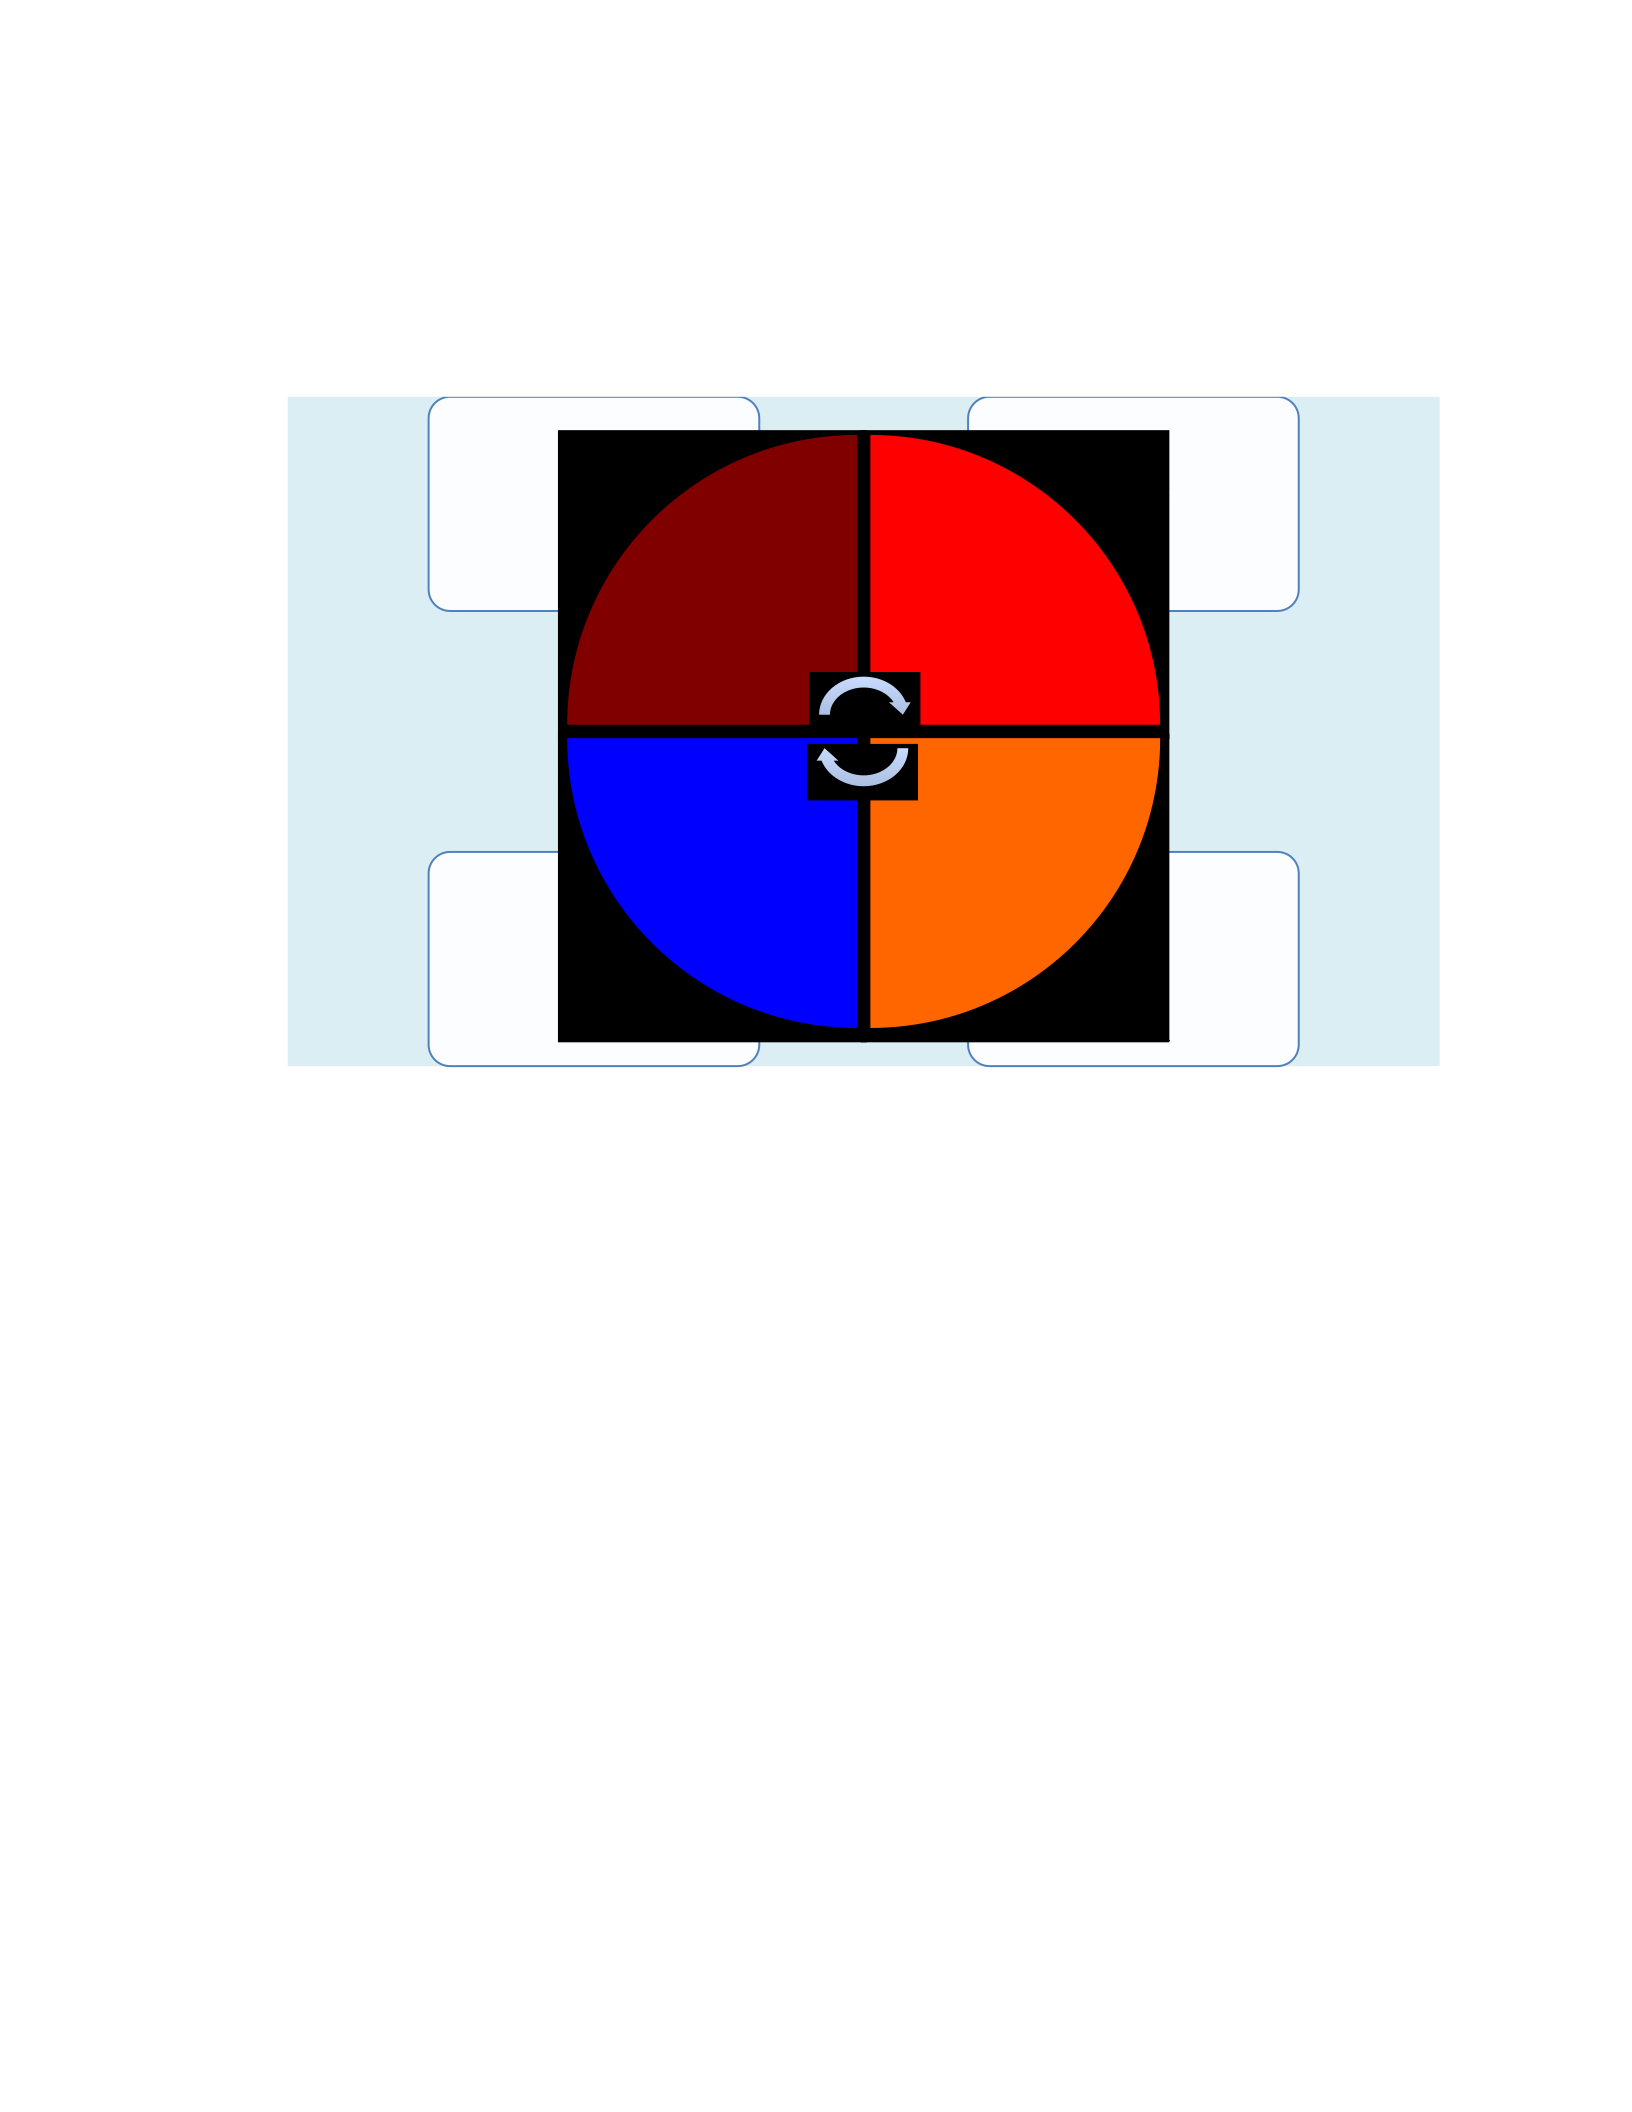
41
below in a diagrammatic form. The diagram depicts the dynamic interplay of the forces
and influences at work.
Figure 7. Anticipated outcomes of participatory engagement.
The outer squares represent the various dimensions of the problems and the inner circles
represent the available potentially collaborative resources and outcomes.
Literature Review
In developing the framework and variables for this research study, a total of 108
scholarly research papers were reviewed. These research articles were from all parts of
the world and addressed many dimensions of the challenge posed by diabetes in the
contemporary world. While reviewing literature, I considered the following factors
specifically: First, the resonating theme of the research alongside key learning’s and
messages; Second, the research methodology and theoretical framework chosen by the
researchers; Third, the key connect points of the reviewed literature with the proposed
• Diabetic!
patients!and!
the!
community!
• The!
degenerative!
consequences!
of!diabetes!
• Paucity!of!
trained!
medical!
professionals!
• The!emerging!
diabetes!
pandemic!in!
India!
M !
M !
P !
T !AYUSH!
P !
P !Health!
P !
M !
H !
O !

42
subject of this study; and lastly, the insights offered by the research in terms of challenges
that were relevant to my study.
Five broad resonating themes from the literature reviewed were identified. The
first theme was that diabetes is a complex multifactorial disease and much remains to be
done in medical and scientific terms to explain its causation and find a permanent cure
for the condition of various types of diabetes. The second theme was that the incidence of
this disease is much larger than estimated because of extensive non-diagnosis in all parts
of the world and non-inclusion of high-risk prediabetics in the count. The third theme
was that diabetes is a life-changing phenomenon for the patient and the family and also
the nation’s healthcare system and therefore the educational and support needs of the
patient and community need to be well provided. The fourth theme was that innovative
solutions like the one proposed in this dissertation are well worth exploring to tackle the
emerging pandemic of diabetes in India. The fifth theme was the potential benefits of
using complementary systems of medicine to address diabetes. Literature supported the
continued quest for breakthrough or disruptive methods and innovations to help tackle the
challenge of emerging diabetes pandemic in India and the world.
The five themes from the reviewed literature are discussed in detail below and
again in the later part of this study to relate the themes to the findings of my research.
Complex Multifactorial Disease, a Challenge Unmet to Date
Mannino and Sesti (2012) used individualized therapy for Type 2 diabetes
mellitus (T2DM) and tried to summarize the current level of understanding of genetic
polymorphisms of anti-diabetic treatment that tend to affect the responses of diabetes

43
patients and study subjects in the context of their own diabetic health condition. Mannino
and Sesti opined that commonly used therapies in the management of T2DM include
anti-hyperglycemic agents soon after the disease is diagnosed. The other commonly used
lines of treatment include metformin, sulfonylureas/glinides, dipeptidyl peptidase-4
(DPP-IV) inhibitors, GLP1 mimetics, and thiazolidinediones. Mannino and Sesti (2012)
argued that over time it has become abundantly clear that most diabetic patients do well
to have more than one anti-diabetic drug. Mannino and Sesti (2012) also found and
reported that there is considerable variation among individual responses to the
administered pharmacologic line of treatment for diabetes. Mannino and Sesti (2012)
built their argument by stating that proven and well-established lines of treatment
produced different impact on different people because of genomic variations among
patient population. Mannino and Sesti (2012) posited that the quest to discover genetic
components that are capable of improving the effectiveness of treatment response
continued to be a key objective of medical and scientific community.
The twofold objectives of drug development listed by Mannino and Sesti (2012)
were treatment of the medical condition and avoidance of side effects and related
complications. After an exhaustive review of literature, Mannino and Sesti (2012)
concluded that relatively small number of genes and polymorphisms had been associated
with changes in drug response and disposition and ingestion, or interaction with the target
genes and peptides that are known to impact the diabetes in human body. Mannino and
Sesti also found and reported that only few of the results were positive and in many cases
the variability was high.

44
Researchers Cakan, Kizilbash, and Kamat in their seminal study published in
2012 in the Journal of Clinical Pediatrics brought out a very important trend that is
challenging the commonly held view that Type 2 diabetes is an adult phenomena and
Type 1 diabetes is a juvenile phenomenon that impacts only small children. Cakan et al.
(2012) showed that the conventional history of diabetes among children is changing. The
symptoms and characteristics that once were a hallmark of Type 1 diabetes were being
increasingly seen in Type 2 diabetes and other forms of diabetes. Cakan et al. also
showed the challenges of diagnosis and classification of diabetes faced even by
experienced endocrinologists (2012). The Cakan et al. (2012) theme was that the
classification of symptoms among various types of diabetes has become more complex
and needs further scientific attention and support (2012).
Cakan et al. (2012) posited that the classification of diabetes was no longer a
straightforward process and that the patient symptoms witnessed in insulin-dependent
juvenile diabetes and insulin-independent adult diabetes were not as simple and
straightforward any more. Cakan et al. (2012) argued that the initial classification of
diabetes among children was based on the classical paradigm that sick patients with
higher levels of glycated hemoglobin HbA1c and diabetes ketoacidosis represented Type
1 diabetes. Cakan et al. (2012) submitted that this paradigm does not stand the scrutiny of
changing character of diabetes as applying old standards had started leading to growing
incidence of misclassification. Cakan et al. (2012) also held that patients who are at the
greatest risk of misclassification were those with Type 2 diabetes and high values of
HbA1c and ketoacidosis. Cakan et al. (2012) showed that about 10% of the studied

45
patients were misclassified and concluded that the primary classification of diabetes may
not necessarily be accurate and the clinical diagnostic data may not be a reliable
determinant of the class or category of diabetes. This research may have far reaching
consequences on detection and diagnostic process currently deployed for determining
existence and classification of diabetes and thus its treatment.
Cakan et al. (2012) have added a new layer of complexity to the debate on
diabetes. Cakan et al. posited that the popular distinction between Type 1 and Type 2
diabetes had developed complex overlaps and healthcare professionals did not see it as a
straightforward distinction as it was in the past, any longer. The increased number of
people with diabetes in India and the added complexity as revealed by Cakan et al.
(2012), suggest that there is an urgent need to address overlapping complexity of Type 1
diabetes and Type 2 diabetes and adds to the Indian phenomenon of emerging diabetes
pandemic. The integrative combination of the modern and traditional approaches to
diabetes might have to factor in the concerns raised in the Cakan et al. (2012) research
study. The distinction is critical to decide the line of treatment for the patient and to
ensure targeted outcomes.
In their long duration diabetes study in The Netherlands, researchers Riet, et al.
(2012) aimed at creating a research superstructure to gain deeper insights into risk factors
of diabetes including the genomic determinants and biomarkers associated with diabetes.
The Riet et al. (2012) study was based on a cohort of 7,000 Type 2 diabetes patients
studied between the years 2009 and 2012. The study was very comprehensive as it
covered all the medical centers attached to all eight universities in The Netherlands. The

46
study was a part of the string of pearl initiatives that was based on combining the strength
and resources of all the universities and their medical facilities in the country. The
methodology used in this study was an observational cohort study. The data collected for
all participants included demographics, clinical parameters and health assessment topics
including genome information for future research (2012).
As was seen in the longitudinal study of Donald et al. (2012) in Australia, the
Riet et al. (2012) narration of the efforts made in The Netherlands reinforced the strength
of argument that much remained to be done in understanding the entirety of the life cycle
of diabetes. Long-term studies, such as the ones reported by Donald et al. (2012) and Riet
et al. (2012) promised to bring more clarity to the lifecycle of diabetes and to map the
progression of disease in the lives of patients. The outcomes of these long-term studies
will be valuable for all countries including India that are continuously developing and
fine-tuning their public health strategy to address the complex and multiple challenges
posed by diabetes. Maull et al. (2012) in their review article based on conference
proceedings of 2012 examined the views and research presentations of a large number of
researchers and scholars to study possible correlation between diabetes and heavy metals
in general and arsenic specifically. They reviewed the evidence both from human and
animal studies. Of specific interest to Maull et al. (2012) were the data from countries
where arsenic content in water is generally found to be present either in moderate or
excessive quantities. The data reported in the study came from Bangladesh, Taiwan,
Pakistan, Mexico, Turkey, Spain and United States (Maull et al. 2012).

47
Maull et al. (2012) found that there is credible though not conclusive evidence to
suggest that there is some correlation between presence of arsenic in the body and onset
of diabetes. Maull et al. (2012) suggested that the available evidence is adequate to
inspire researchers from proceeding further to investigate the linkage between heavy
metals and diabetes. The researchers posited that heavy metals could come in to human
body either through water and food or through a host of other environmental factors
including the air that we breathe. The authors also tried to distinguish between organic
and inorganic arsenal. Maull et al. (2012) noted that marine life and thus marine food
intake may be an important source for arsenic to find its way into human body. Maull et
al. (2012) provided a detailed analysis of data generated from the large cohort study in
Bangladesh where correlation arsenic and diabetes also factored in the water and food
consumed by the cohort with possible arsenic content (2012).
There are many areas in the Indian subcontinent where water is reported to have
arsenic content (Majumdar & Guha, 2012). In addition, the populations living along the
several thousand miles coastline of Indian peninsula have fish and other marine foods as
a staple for people residing in coastal areas (2012). If the hypothesis of linkage between
intake of arsenic and onset of diabetes were validated (Maull et al., 2012), this factor
would have significant implication on what India might need to do come to terms with
the magnitude of challenge posed by the emerging diabetes pandemic. Separately,
Kyizom, Singh, Singh, Tandon, & Kumar (2012) shared the research findings on role of
diabetes in adversely impacting the central nervous system. Thus arsenic contaminated

48
water may cause diabetes (Maull, 2012) and a chronic diabetic condition runs the risk of
damaging a patient’s central nervous system (Kyizom et al., 2012).
Incidence of Diabetes, Larger Than Ever Estimated
In the study of British citizens of Bangladeshi descent, Alam et al.’s (2012)
comments resonate very well with the subject of my research. The South Asian diaspora
is genetically more prone to diabetes and therefore more vulnerable to the consequences
of disease (2012). This combined with scarcity of resources makes a formidable
challenge to meet in the entire developing world including India where diabetes has
assumed the scale of an emerging pandemic. In a study protocol, published in the Biomed
Central Public Health in 2012, Donald et al. declared the immensity and magnitude of
the scourge of diabetes. Donald et al. (2012) described this as a major global challenge of
public health in Australia and the rest of the world. Donald et al. also stated that diabetes
presents a very significant disease burden and cost even in a developed country like
Australia (2012). It was revealing to see that no part of the globe had escaped the
incidence of diabetes. Jayawardena et al. (2012) in their meta-analysis on the incidence of
diabetes in South Asia also concluded that the incidence of diabetes in the Indian
subcontinent is significantly larger than estimated by public health authorities.
Researchers Skoro-Kondza et al. (2009) made similar assessment of diabetes in
the United Kingdom. Skoro-Kondza et al. (2009) posited that Type 2 diabetes in the
United Kingdom had reached epidemic proportions and both the cost and incidence are
on continuous ascent. Bogner et al. (2012) in a study on the U.S. diabetic population
reported the beneficial results of combining medication with educational inputs. The

49
patient group in this study had symptoms of depression, which was a much-observed co-
morbidity for diabetics (2012). The patients who received educational guidance in the
form of diet, lifestyle and motivation alongside medication showed much better
compliance in going through the treatment at their homes. The role of education,
motivation and counseling were very well proven and established in the study reported by
Bogner, Morales, de Vries, & Cappola (2012).
Life-Changing Phenomena Seeking Support and Guidance
Donald et al. (2012) studied the overall picture of diabetes on a cohort of about
4,000 Australians in the Queensland region over a period of five years. The focus of the
study designed by Donald et al. was on how people live and cope with the challenges
posed by the disease. The first round of data collection on parameters listed below was
done in 2008 with an annual round of data collected every year thereafter. The
parameters measured by the researchers included demographics, lifestyle factors and
health characteristics, and disease incidence, quality of life indicators, the emotional
wellbeing of the patients, and the efforts made towards self-management of the disease.
Donald et al. (2012) also measured the utilization of the healthcare resources provided in
the region and the assessment of the patients towards quality of care. Donald et al.
(2012) invited over 15,000 diabetes patients in Queensland that were enrolled with the
National Diabetes Service Scheme to join this five-year study. The study invite was
accepted by 29% of the invited patients. Though only a third of the patients participated
in the study, the study provided high quality data to understand trends and patient

50
responses to this chronic disease. The authors (2012) validated the fact that 4.4% of the
Australian population was diabetic.
Namak and Cremer in their 2012 review of four meta analyses collated the results
of a number of studies that had sought to analyze the impact on diabetic health of patients
who use self managed blood glucose (SMBG) devices at their homes. The authors
concluded that patients who regularly use SMBG devices at home showed marginal
improvement in their glycated hemoglobin levels versus the control group that did not
use any self-monitoring devices (2012). Namak and Cremer (2012) also found that these
benefits did not extend over a 12-month period though gains were seen in the 6 months
horizon. The limitation of this meta-analysis was that data size was small and the
research had to rely on tardy compliance in data reporting by the patient population.
The authors of the meta-analysis (2012) also showed that more frequent use of
SMBG devices did not necessarily result in better results. So as not to contradict the
guidelines established by the ADA, Namak and Crater (2012) summarized the current
state of advisory.
The American Diabetes Association advocates SMBG as a guide for patients who
use oral or medical nutrition therapies for diabetes. Patients should receive initial
instruction in SMBG and routine follow-up evaluation of their technique and ability to
use data to adjust therapy. The American Association of Clinical Endocrinologists
(AACE) advises that SMBG can be initiated at the same time as medical therapy,
lifestyle modification, specific diabetes education, or dietary consultation. If HbAlc
levels are above target, the AACE recommends more frequent SMBG: preprandially, 2

51
hours postprandially, occasionally between 2 am and 3 am, during illness, or anytime a
low glucose level is suspected (ADA, 2012).
Kosti and Kanakari in their 2012 study done in Greece evaluated the status and
role of education in diabetic patients testing the hypothesis if levels of education about
the disease impacted the health outcomes of the patients. Kosti and Kanakari (2012)
posited that if patients are better informed of the causes, consequences, and preventative
aspects of a health condition, they possibly have greater confidence and ability to manage
that health condition. Kosti and Kanakari (2012) opined that diabetes is a multifactorial
disease that impacted both “physical and psycho-social dimension of each patient”. They
reviewed published literature for the period of 1999-2012 using the PubMed database and
searching on terms “diabetes mellitus”, “self management” and “education”.
Kosti and Kanakari (2012) made a pertinent observation that diabetes was not a
disease of modern society as mistakenly believed but a very old health condition that was
referred to as early as 2nd century BC by Greek physician Aretaeus. Physician Aretaeus
had described symptoms of a disease that fully matched the symptoms of diabetes as are
known now. This was separately confirmed in the traditional Indian Ayurveda system,
the origin of which is pegged between 5,000 and 10,000 years ago where the disease
madhu-meh (diabetes) had been discussed in detail. The key point emerging from this
analysis is that diabetes is possibly as old as human civilization and has always afflicted
humans in all parts of the world. A significant percentage of mankind has always been
impacted by diabetes. The current levels and scales though are unmanageably large.

52
Kosti and Kanakari (2012) posited that despite such an ancient heritage and
existence, diabetes as a disease, its causes, treatment, and consequences have still not
been fully mapped. Kosti and Kanakari (2012) concluded that patients who received
education and information about the management and care of disease reported better
health outcomes than those who did not receive the benefit of any such education. They
recommended the best time to start patient diabetes education is when HbA1c scores are
high to best manage the early symptoms and prevent it from becoming a chronic
condition (Kosti & Kanakari, 2012). They also found that close involvement of patients
and care providers played a critical role in self-education and self-management of
diabetes. The authors (2012) submitted that effective and efficient communication had
been demonstrated to show favorable influence of patient decisions about the health
behaviors and practices associated with the desired and eventual health outcomes in case
of diabetes. Kosti and Kanakari (2012) summarized their conclusions in saying that
education was a very worthwhile investment for the patients as also the health
professionals in order to promote and improve the quality of life of people with diabetes.
The conclusions reported in the Kosti and Kanakari (2012) study merit support.
Education regarding management and living with diabetes is critical for every patient
upon diagnosis. (2012). In a country like India, where literacy levels are still low and
people tend to rely on hearsay rather than authentic facts (Shetty, 2012). Improved patient
education could become a very significant outcome of combining the benefits of
traditional and modern systems of medicine in containing the emerging pandemic of
diabetes. Merkel and Wright in their 2012 article about the lives of parents with children

53
that are born with type 1 diabetes examined the importance of support systems required
to help the families live with the reality of life long condition for their children. They
used an evidence based model to demonstrate the beneficial impact of a web based tool
that would help parents access ‘how-to’ and ‘what to’ knowledge in an easy and friendly
manner. Merkel and Wright (2012) showed that there is a significant knowledge gap on
diabetes for all stakeholders, whether they are for adults who become diabetic or parents
of children who are born with diabetes.
Chew et al. (2012) focused on the incidence of concomitant hypertension among
the Malaysian diabetes patients. Chew et al. (2012) reported that there were 70,889 new
patients of diabetes in Malaysia in the year 2009. Over half of these patients were
hypertensive with the women of Malay ethnicity forming the majority of both of the
diabetics and those that also had hypertension. Chew et al. (2012) concluded that a
possible reason for high concomitant hypertension might be delayed diagnosis and
obesity among the ethnic Malay patients.
The Chew et al. (2012) thesis was indicative of two clear challenges for India that
has significant well-reported incidence of under-diagnosis. The longer the delay in
diagnosis of diabetes, the greater is the likelihood of co-morbidities setting in (Shetty,
2012). This also indicates a significant danger for the economic burden of the disease.
The scenario in Malaysia is thus very similar to India. Both Malaysia and Indonesia also
have widely prevalent native medical traditions that do not work in tandem with the
public health agenda or priorities of these countries. The native traditions in Malaysia and
Indonesia work independently of the modern medical processes, as in India. Wung & Lin

54
in their 2012 study on gestational diabetes mellitus reported that over 135,000 pregnant
women in the United States faced the health condition of glucose intolerance during their
pregnancy with the incidence higher among Asian Indian women versus the Whites,
Blacks and Hispanics (2012). Wung and Lin (2012) also reported that the incidence of
gestational diabetes has increased worldwide and is now considered as one of the major
complications of pregnancy, impacting both the mother and the child, both during and
after pregnancy. Wung and Lin (2012) observed that higher levels of body mass index
greatly increased the risk of complications and captured in their study the work done on
genes that might be behind this phenomenon.
The reviewed genes were classified into three groups: genes that affect insulin
secretion, genes impacting insulin resistance, and genes that influence mitochondria
functionality. Wung and Lin (2012) also found that zinc played an important role in
regulating production and storage of insulin in the body and recommended continued
research to help understand the causes of gestational diabetes, which in turn would help
find cure for the condition.
The Wung and Lin (2012) study is relevant for India as the incidence of
malnutrition and micro-nutrient deficiency delayed diagnosis in India with attendant co-
morbidities is very high (Mohan et al., 2007). In the Wung and Lin (2012) study as well,
the incidence of gestational diabetes was highest among the Asian-Indian origin women
in the United States and the ethnic Asian-Indians form the highest risk group. This
suggests that incidence of gestational diabetes in India could possibly be high and needs
to be mapped in order to help both the mother and the child (Mohan et al., 2007).
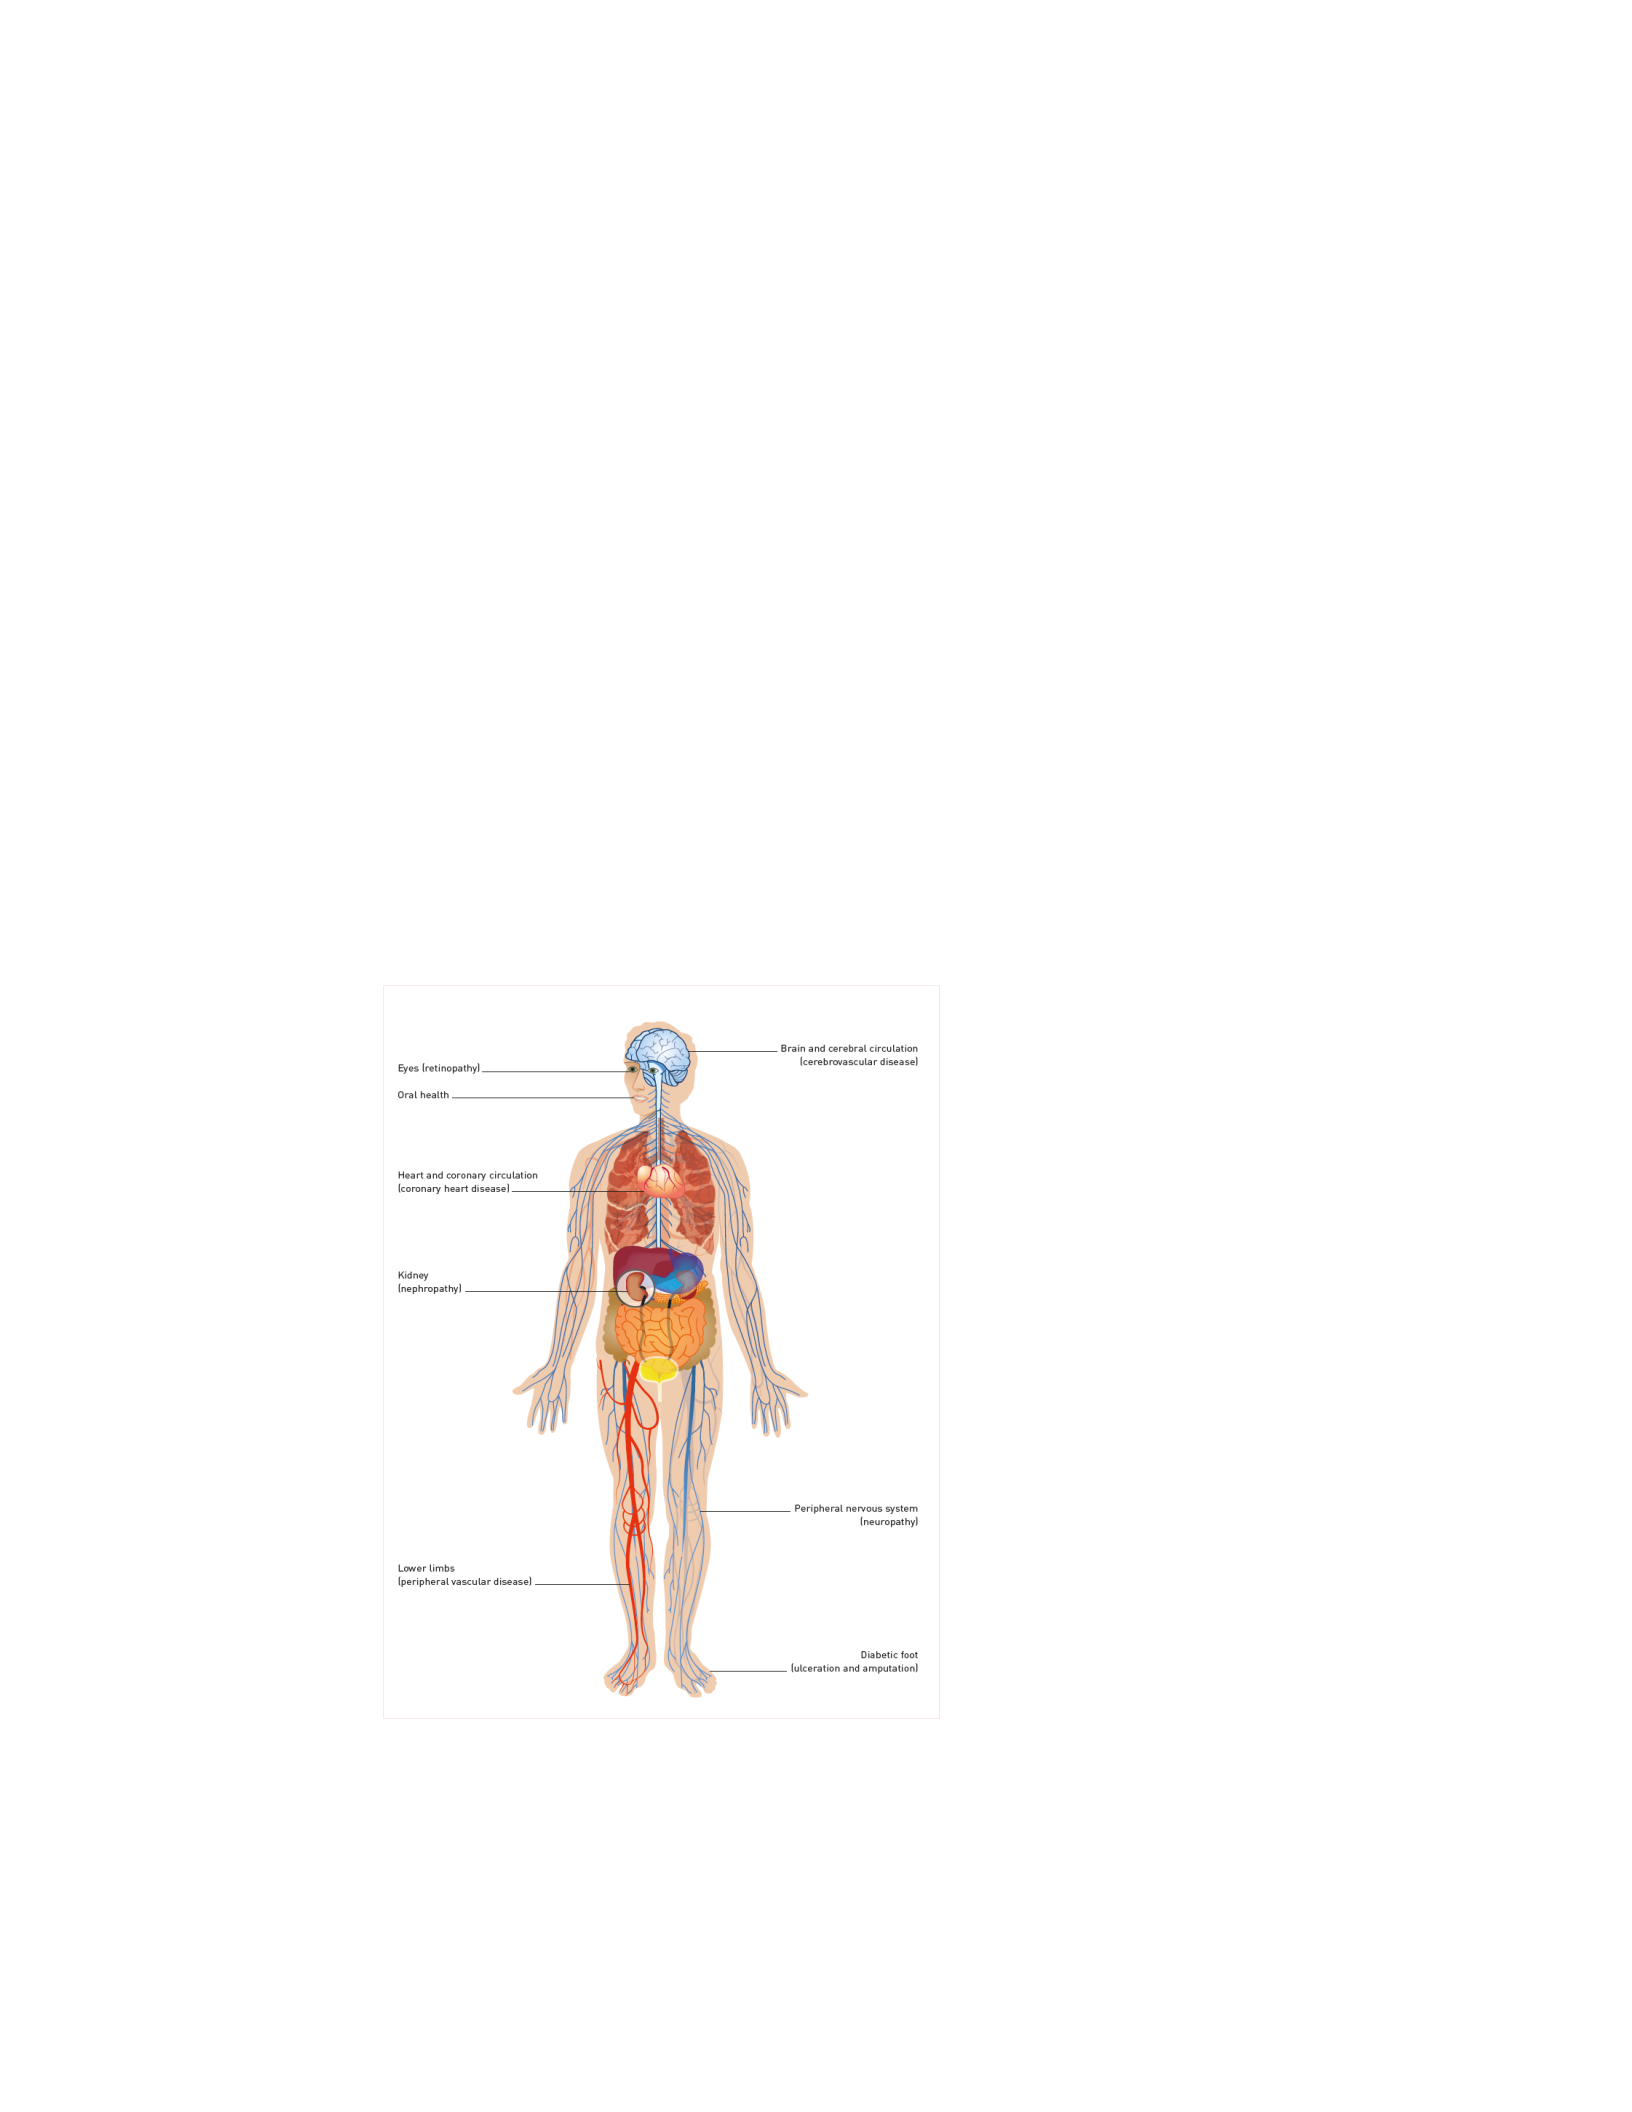
55
Norris et al. (2012) reported that many normal growth parameters like height,
weight, and head-circumference are severely impacted in the down lineage of the diabetic
populations (2012). Patel et al. (2011) highlighted that progressive introduction of
universal health insurance in India will help in multiple ways. Universal health coverage,
Patel et al. (2012) argued will lead to better and timely diagnosis, and treatment of
diabetes. Penn et al. (2009) reported similar conclusion in Europe that timely
intervention could prevent impaired glucose intolerance from degenerating into diabetes.
Unattended, undiagnosed, untreated or undertreated diabetes can result in serious health
consequences. This has been graphically captured by IDF and explains the possible
consequences of diabetes on various organs and systems of human body.
Figure 8. Consequences of diabetes for human body. From Global Diabetes Atlas (6th
ed.), by the International Diabetes Federation, 2013. Retrieved from
http://www.idf.org/sites/default /files/ The_Global_Burden.pdf

56
Definitive Role for Innovative Solution
Donald et al. (2012) in their study in Queensland, Australia were confident that
their ‘living with diabetes study’ would bring out a very comprehensive picture that
would be valuable for the policy planners to help them design public health solutions and
strategy. Donald et al. (2012) examined longitudinal data (2008-2013) on diabetic
parameters like HbA1C (glycated hemoglobin), to present a fair and accurate picture of
reality. The researchers were of the firm conviction that the completed conclusions of the
study would be very valuable. It is important to have longitudinal studies like the Donald,
et al., study (2012) to understand how people cope with this chronic health condition and
what kind of complications it may lead to with the advancement of patient’s age.
Mannino and Sesti (2012) also recommended that continued gene profiling was required
to ensure successful pharmacogenomics conclusions on need for more individualized
treatment for diabetic patients. The researchers also held that more work was needed to
establish the impact of ethnic variations in pharmacogenomics response to the treatment.
Researchers Mannino and Sesti (2012) were successful in drawing attention to the
fact that diabetic patients respond very differently to established therapies and lines of
treatment and in the lifetime of a diabetic multiple lines of treatment were tried. This
supports the assertion of my research that it might be more prudent and effective to
combine the modern and traditional systems of medicine to help the diabetic population
both from the point of view of outreach as also efficacy of treatment. Namak and Cremer
(2012) challenged a commonly held belief that diabetic’s health would improve if they
use self -monitoring devices at home.

57
While the self -monitoring devices help in providing rapid measurement of level
of blood sugar, they do not necessarily lead to changes in longer-term measures, as
established by the HbA1C test, which is a measure of blood glucose levels over a running
period of 90 days (Namak & Cremer, 2012). Namak and Cremer (2012) have done well
to highlight the importance of continuous monitoring of diabetes by more authentic
processes. The do it yourself devices can be used, as stated in the ADA advisory (2012)
as an indicative tool, at best. The sales of glucometers and other similar devices in India
have been rising and the health authorities should not draw any comfort from this fact, as
these devices, as observed by Namak and Cremer (2012) may not lead to mitigation of
the disease. While SMBG devices may be of some value to the patients, these have no
significant implications for policy planners as stated in the research findings of Namak
and Cremer (2012).
Keating (2012), in his review of Insulin Detemir, as the primary treatment therapy
where insulin fortification is required by the body, presented experience and evidence of
Insulin Detemir emerging as a favored line of treatment compared to the other
alternatives. Keating (2012) presented a number of health conditions and sub conditions
of diabetes where Insulin Detemir had been used as the experimental therapy and some
other offerings (oral medications) as the control. Keating reported that in most if not all
the conditions, Insulin Detemir came out as the choice medical treatment for basal
application of insulin on account of superior glycemic control capability (2012). Keating
expressed his satisfaction that Insulin Detemir as the slow acting insulin treatment created
favorable results across applications and line of treatment and recommended it as the

58
preferred method of insulin supplementation in patients of Type 1 diabetes and
sometimes in Type 2 diabetes patients as well (2012).
Keating (2012) acknowledged that while the global battle against diabetes was not
close to being won, there are treatments and solutions available for diabetics that need
insulin support for living, that safe methods are available to manage their health
condition. In the context of India, use of Insulin Detemir has to be examined for
economic considerations and affordability by the patient population. Insulin dependency
is a serious health condition and the cost of treatment would make it a serious challenge
for the underprivileged people to come to terms with. Vajen, Holt, Marx, Schwartz &
Shubrook in their 2012 study carried out in Ohio, United States with 245 patient-residents
in extended care facilities, compared standards of home care for the diabetics with the
ambulatory standards prescribed for their care. Vajen et al. (2012) concluded that while
some gaps between home care and formal care environment were to be expected, the gap
could have serious consequences for the affected patients. Vajen et al. (2012)
recommended that the American Diabetes Association should develop new standards and
guidelines for patients undergoing extended homecare in nursing homes or similar quasi-
medical institutions.
The observations made by Vajen et al. (2012) confirm that there is considerable
scope for improving patient care practices for diabetic patients in the extended care
system (2012). The institution of nursing homes in India is very prevalent (Mohan, 2007)
and the data from Ohio and West Virginia captured by Vajen et al. (2012) might be
applied to the conditions in India as well. Tandon, Ali and Narayan (2012) in their study

59
published in the Journal of Cardiovascular Drugs presented their findings on the linkage
between high levels of HbA1c and cardiovascular risk. Tandon et al. (2012) confirmed
that controlled levels of blood sugar lowered the attendant risk of heart disease but it was
difficult to say at what level this occurred. Tandon et al. (2012) agreed with the
observational data and analyses emanating from the United Kingdom Prospective
Diabetes Study (UKDS). Tandon et al. (2012) also referred to three clinical trials done in
recent times that tallied with the observational data presented by the researchers.
The highlight of the Tandon et al. (2012) study was that it is important to control
levels of blood sugar to lower the risk of heart disease. Avoiding diabetes wherever
possible and managing diabetes where avoidance was not possible could only ensure this.
This would have to be achieved through a comprehensive national diabetes management
program in India that is more inclusive than all the existing initiatives. Munt and Hutton
(2012) from Australia conducted research on self-management of type 1 diabetes. They
(2012) argued that while patients with type 2 diabetes were able to successfully manage
their health condition with self-care, they wanted to examine if it was possible to do
likewise for Type 1 diabetes patients inside or outside a professional health care
environment (2012). Munt and Hutton (2012) concluded that there was a subtle but
important difference between professional and expert care and a Type 1diabetes patient
can be at best an expert but not a professional. In addition, Munt and Hutton (2012)
concluded that while it was good for a Type 1 diabetes patient to have expertise for self-
care, the Type 1 diabetes patients must not try to replace the professional care in a
hospital environment with self-help.

60
The implication of Munt and Hutton’s (2012) research demonstrated that for
management of diabetes the professional support super structure is critical and must be
adequately provided for by the Indian healthcare system. Diabetes is a serious health
condition, particularly Type 1 and must be handled with utmost care.
Gong et al., (2011) in their six year lifestyle intervention study in China found
that the incidence of comorbidities like retinopathy among patients that had IGT was
47% lower than those that did not make any lifestyle changes to manage prediabetes or
diabetes health conditions. Even simple innovative solutions like guidance on lifestyle
intervention made a significant difference in the outcomes (Gong et al., 2011). Rani et al.
(2009) highlighted the much-observed phenomenon of retinopathy in rural India tracing
its origin from under treated or untreated diabetes (2009).
A similar finding was reported in the Mayor (2012) study where Mayor
summarized the potential beneficial impact of following IDF recommendations in the
management of diabetes (2012). Mayor (2012) rated IDF as a significant positive
influence in drawing the attention of global policy makers on the incidence and steps
required to control the growth rate of diabetes. The IDF (2013) has explained the
physiology and anatomic process that lead to risk of comorbidities in diabetes in the
figure below.
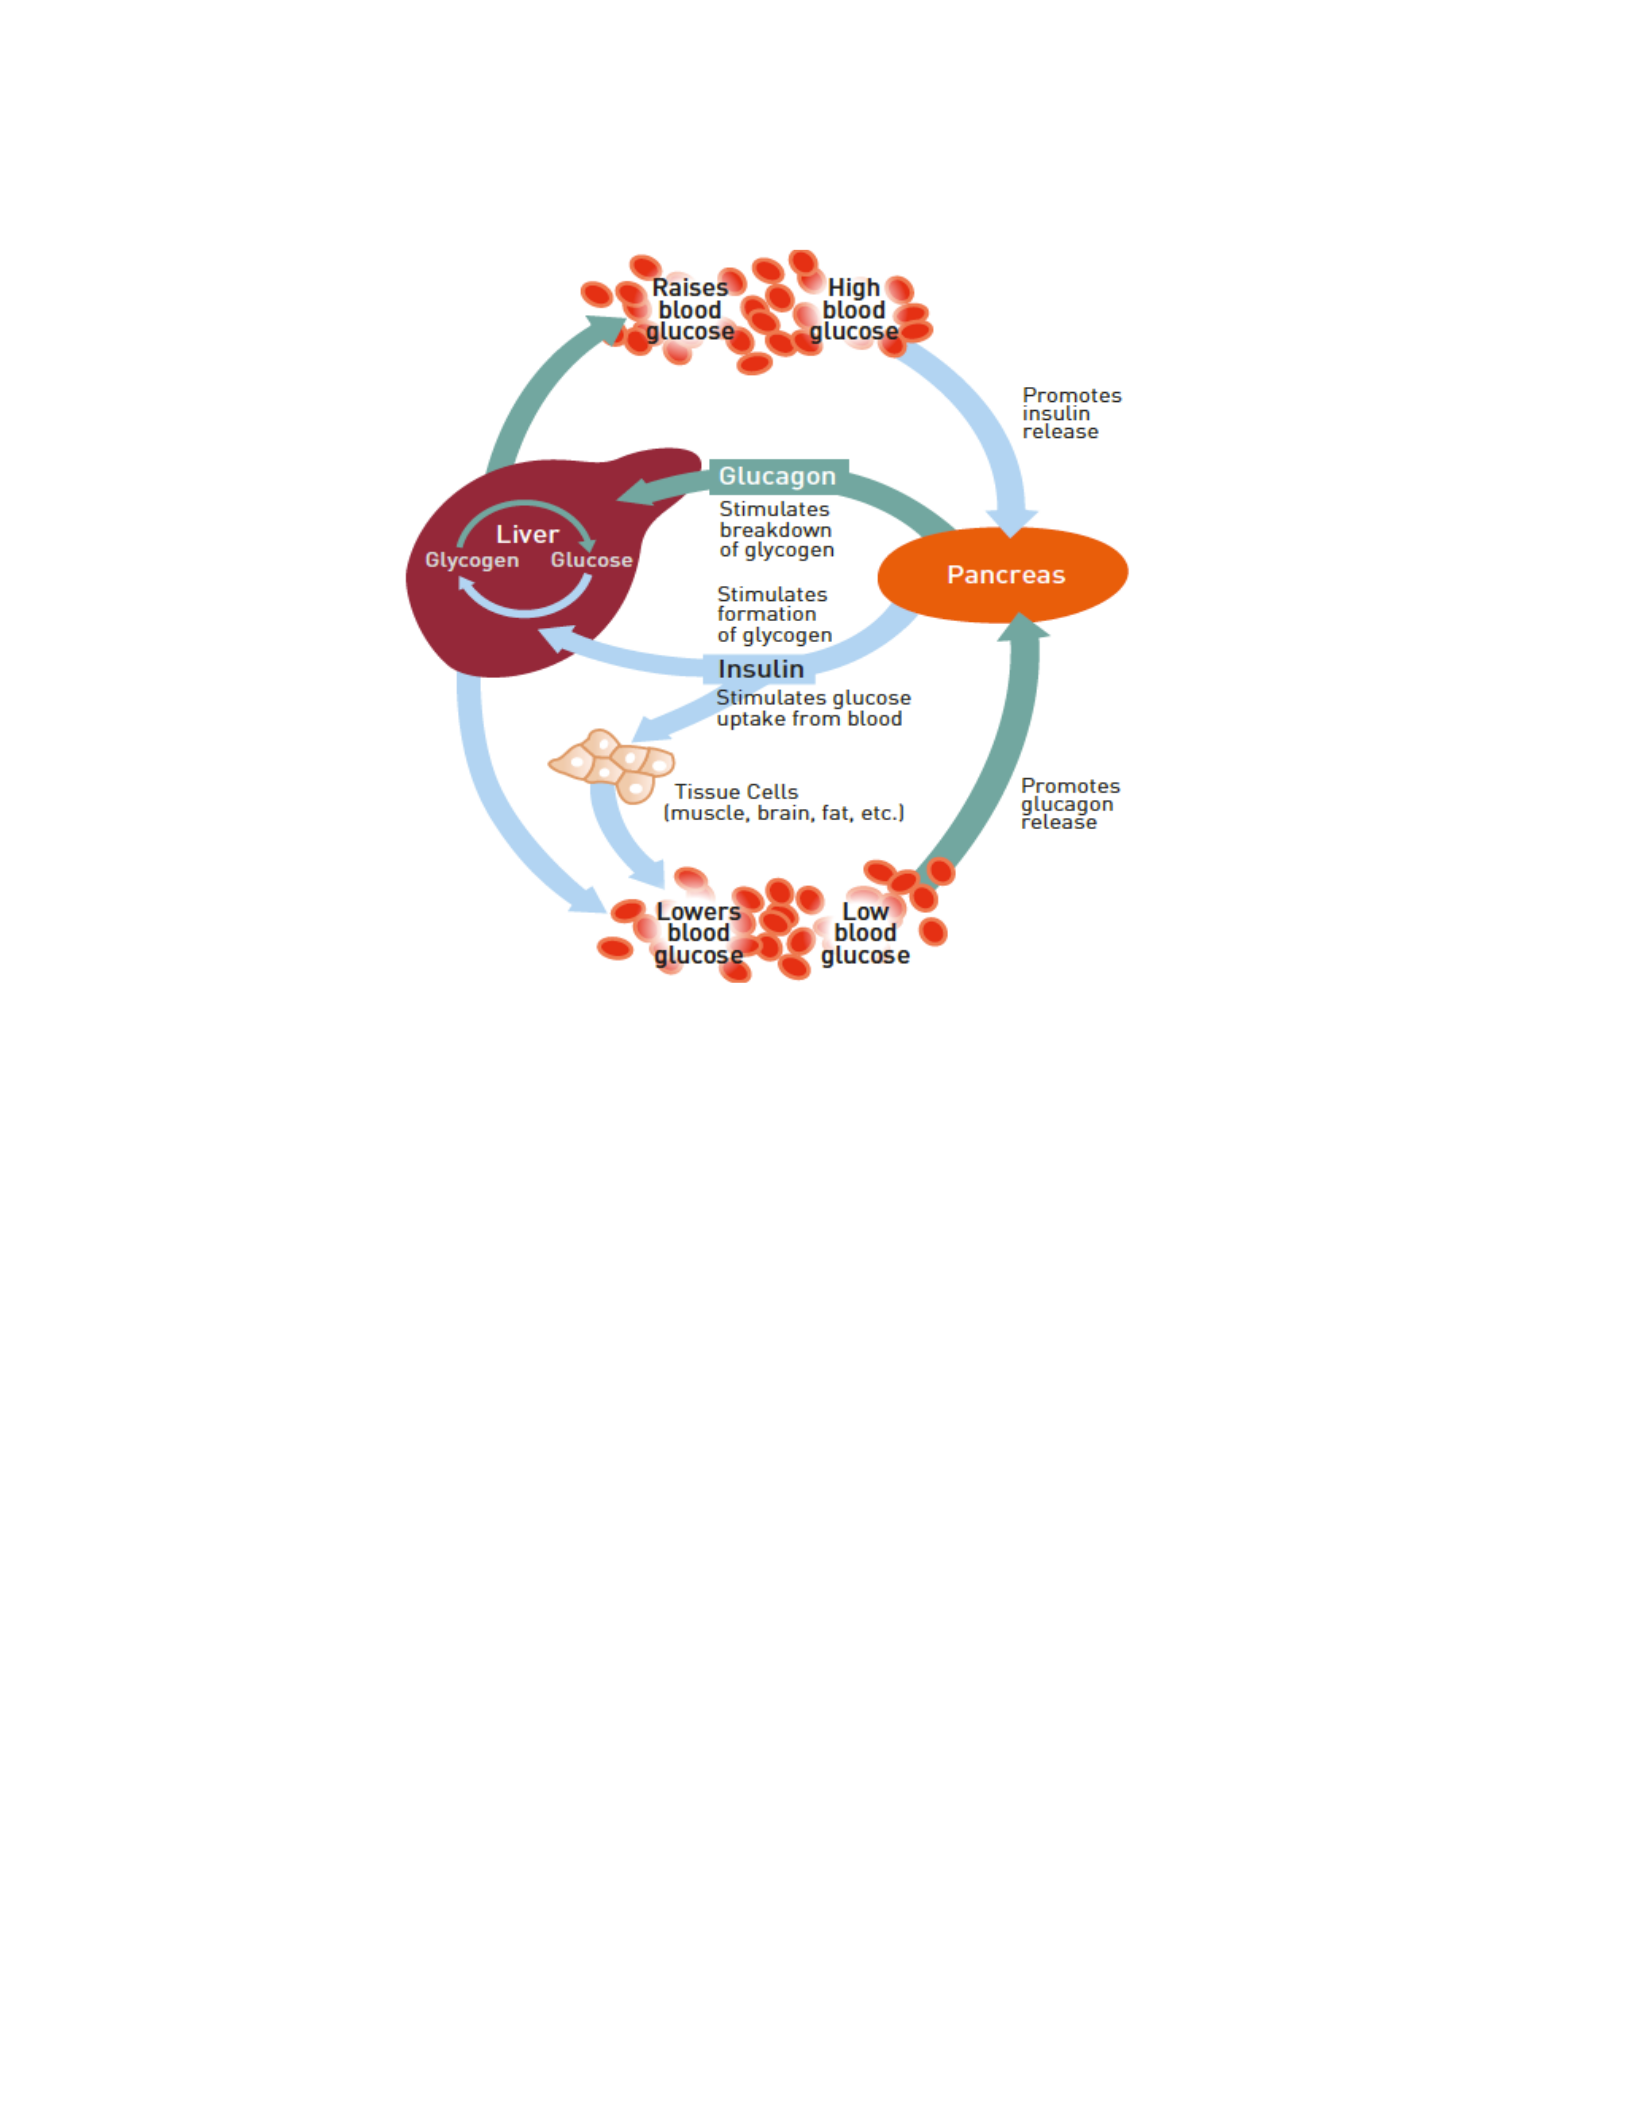
61
Figure 9. Pathology and physiology of diabetes. From Global Diabetes Atlas (6th ed.), by
the International Diabetes Federation, 2013. Retrieved from http://www.idf.org/sites
/default/files/ The_Global_Burden.pdf
Complementary Health Traditions
Researchers Skoro-Kondza, Tai, Gadelrab, Drincevic, and Greenhalgh (2009) in a
study conducted in United Kingdom attempted to estimate the impact of yoga on
reducing the glycated hemoglobin levels of diabetic patients. The starting hypothesis of
their research was that there was evidence to suggest that regular practice of yoga might
lead to lower levels of HbA1c. The experience reported by Skoro-Kondza et al. (2009)
was that as yoga was not a native school of medicine in United Kingdom, the number of
participants recruited in the study was sub-optimal and most of the recruited patients did
not continue with the prescribed yoga practices at their homes. Skoro-Kondza et al.

62
(2009) noted decline in HbA1c values among the group of patients that practiced yoga
more diligently. Though the value was not significant statistically speaking, it provided a
glimmer of hope that alternative therapies and complementary methods like Yoga, if
practiced seriously may help change the health outcomes of diabetes patients (2009).
The redeeming feature of this study in the Indian context is that yoga is native to
India and is viewed respectfully as a method for regulating and obtaining good health
outcomes. Yoga costs very little to practice other than the fee that a patient might pay to a
yoga instructor. The Skoro-Kondza et al. (2009) study offers a positive hope for India for
deploying yoga as an active intervention strategy, both to prevent incidence of diabetes
and to manage the diabetic condition. The exploratory randomized control study of
Skoro-Kondza et al. (2009) was a step in the right direction to support the case for
alternative methods and complementary health traditions. The authors reported a positive
directional effect of yoga and yogic breathing on the cognitive health function of diabetic
patients. They concluded that patients that were included in the yoga and breathing group
plus medication versus the group that was on medication alone, showed improvements in
their cognitive health parameters (2010).
Type 2 diabetes is known to impact cognitive health as a co-morbidity parameter,
as reported earlier in the literature review and it was good to see that it is possible to
achieve improved management of diabetes, if patients started including yoga exercises
and yogic breathing in their daily regime of treatment. Kyizom et al. (2010) also found
that yoga combined with yogic breathing had favorable impact on the levels of glucose in
the blood stream. The findings of this study (2010) augured well both for prevention and

63
management of diabetes. A similar conclusion was reported by Gordon et al. (2008) for a
study carried out in Jamaica on 77 patients of type 2 diabetes.
Gordon et al. (2008) compared the benefits of yoga with a group on normal
physical training and a group only on medication with no training in their study. The
authors used a large number of parameters including fasting blood sugar and measures of
oxidative stress and showed improvement in the group that was following the yoga
exercises. Considering the economical dimension of practicing yoga there is a compelling
case for India, in my study, to consider a role for drafting yoga practitioners and teachers
into the containment strategy for managing the problem of diabetes. In a commentary on
the Kyizom et al. study (2010), neurophysiologists Kutty and Raju (2010) showed
appreciation for the findings and the promise it held for managing diabetes in India and
the world, particularly in managing the mental co-morbidities and the possibilities of
preventing the occurrence of diabetes itself. Khan et al. in their 2012 study on the health
benefits of Semecarpus anacardium (a popular fruit used in Siddha treatment) reported
results from a rat study.
The authors fed rats a high fat diet using the milk extract of Semecarpus
anacardium for 30 days against the popular diabetes drug metformin and showed that
extracts of Semecarpus anacardium outperformed the popular metformin in relieving
symptoms associated with diabetes. The evidence provided showed the potential of
commonly found medicinal plants in India and other countries that could be used
gainfully to prevent occurrence or for management of diabetes.

64
Ahmed, Sharma, Mukerjee, Ramteke, and Kumar (2013) in a similar study on a
popular Unani (AYUSH) formulation “ Qurs Tabasheer” reported in a controlled rat
study that rats that were placed on Qurs Tabasheer performed better than the rats that
were fed metformin. This traditional Unani formulation comprises of five herbs Tukhme
Khurfa (Portulaca oleracea seed), Gule Surkh (Rosa damascena flower), Gulnar (Punica
granatum flower) Tabasheer (Bambusa arundinasia dried exudate on node) TukhmeKahu
(Lactuca sativa Linn seed). It is interesting to note that while traditional formulations
have been successfully used for treatment of health conditions for thousands of years,
they have not been subjected to the efficacy and safety standards of modern medicine.
Researchers are now filling a gap that will enhance wider application of
traditional medicines in mainstream domain of public health. Li, Qi, Huang, Yamahara,
and Roufogalis (2008) in their study validated the known health benefits of pomegranate
flowers, widely used in Ayurveda and Unani traditions as a cure for diabetes. While the
pomegranate flower has been used for millennia, the pathways of its beneficial results
were never studied or known. The study by Li et al. (2008) helped shed light on what the
beneficial pathways might be. Li et al. (2008) reported that pomegranate flower had
demonstrated ability to activate the receptors that regulate fatty acid uptake and oxidation
in human body and this activation may be beneficial for treatment and management of
diabetes.
Thakur et al. (2009) analyzed the benefits of Chlorophytum borivilianum
Santapau and Fernandes (Liliaceae) also known as Safed Musli, which is a very
significant ingredient in all-major AYUSH systems. The root of this plant contains

65
steroidal and saponins that act as therapeutic agents. Thakur et al. (2009) compared and
shared evidence on this ingredient across traditional and modern systems of medicine.
Thakur et al. (2009) also stated that there is a trend towards using natural ingredients in
new age medicines and lines of treatment. Reporting their research in Pediatric Diabetes,
Dannemann et al. (2008) stated that while use of complementary and alternative medicine
was well established among adults, even children with Type 1 diabetes were found to use
complementary medicine under parental guidance with better than expected results.
Dannemann et al. (2008) reported that 70% women and 54% men in Germany accepted
trying complementary medicine for their respective health condition.
Dannemann et al. (2008) found that parents had little or no hesitation trying
complementary medicines on pediatric patients with chronic conditions like diabetes.
Dannemann et al. (2008) made a subtle distinction between complementary and
alternative therapies. While the parental resistance to complementary therapies was
minimal, the acceptance of alternative therapies varied depending upon the experience of
usage. Nahin, Byrd-Clark, Stussman, and Kalyanaraman (2012) studied the use of
complementary medication by Type 1 and Type 2 diabetes patients on a patient pool of
3,978 adults in the United States. Nahin et al. (2012) concluded that patients with more
complex conditions were more likely to try usage of complementary medication in the
hope that the complementary therapy might help mitigate their problem. Li’s (2010)
study the on effect of Neuragen, a combination of five main homeopathic ingredients as a
treatment for neuropathic pains was reported in BMC Journal of Complementary
Alternative Medicines.

66
The study was done on 60 patients with foot sole pain, a condition caused by
diabetes. The patients that were administered Neuragen were found to have much higher
degree of relief from pain. Li conceded that while homeopathic agents were traditionally
administered singly, there was a move towards combination of agents to achieve better
and faster results. The Snee et al. (2011) study reported the nutritional experiments of
using bitter melon in diet to manage and treat the health condition of diabetes. Snee et al.
(2011) reported the potential role of simple ingredients and home remedies that could be
used by the people with diabetes to improve the quality of their lives. Westman and
Vernon (2008) examined the potential role of reduced carbohydrate intake as a line of
dietary intervention to manage the incidence of diabetes. The Westman and Vernon
(2008) study reinforced the findings of Snee (2011) study that dietary changes and
modifications have an important role in managing diabetes. The dietary tools are very
well stated in the AYUSH tradition and the complementarity of modern and traditional
approaches would thus have many benefits to offer.
Summary and Conclusions
The five key themes identified in the literature set the context for this research
study. The key takeaway from the first theme was that diabetes is a complex
multifactorial disease. Considering the pace of growth of the disease, it is important to
understand more about the disease and the best available methods to prevent its
occurrence and to manage its consequences. The second strong theme was that estimates
of incidence of diabetes and pre-diabetes might be on the lower side and the emerging
pandemic scale of disease is a real cause for concern. The scale of the disease is large and

67
the number of people who have not been confirmed by diagnosis is possibly very large.
The third striking theme was that diabetes is a life-changing phenomenon and both the
patients and their families and the community at large need continuous guidance and
support. There is considerable evidence in the literature to suggest the benefits of this
approach.
The genetic predisposition (Ramachandran, 1992) of diabetes also brings in a
societal context of anxiety dictated by the fact that a certain geographic category of
people share the genetic traits that place them in a fairly similar risk profile of disease
(Grant et al., 2011). Therefore, the social and economic impact of diabetes on the
caregivers and the community at large warrant urgent and immediate attention so as to
ensure that caregivers can focus on providing their professional services.
Diabetes is one of the greatest ever public health challenges and it needs many
innovative solutions to address the multiple levels and scales of the problem (IDF, 2011).
The Reese (2011) study demonstrated the possibilities and experience of innovative
experiments undertaken for managing the diabetes program with lower costs. Reese
(2011) brought out that the scope of innovation is not just limited to science and
technology related to diabetes but also the steps involved in rolling out successful
programs and their pragmatic execution.
The need for constant and sustained innovation in solutions for chronic health
conditions like diabetes was evident in the reviewed literature. All the reviewed research
studies expressed the need for more research to address the many dimensions of the
diabetes challenge. The role of traditional, complementary, and alternative medicines is

68
much larger than what was believed or expected in modern society (Reese, 2011). The
choice of research methodology and design of study ensure that the theme and subject of
research are analyzed and examined rigorously. The rationale for qualitative research
design, the case study method and participatory action research approach used in this
study are discussed in the next chapter.

69
Chapter 3: Research Method
Introduction
The purpose of this study was to assess the practicability of using an integrative
approach as a potential solution for India’s emerging diabetes pandemic. Qualitative
researchers study things in their natural settings, attempting to make sense of or interpret
phenomena in terms of the meanings people bring to them (Denzin & Lincoln, 2011).
The number of people with diabetes in India is far outside the reach of the medical and
economic resources available in the country. Diabetes, as a case with many ramifications,
has to be addressed jointly by physicians, caregivers, policy makers, and people with
diabetes. Understanding the views and perceptions of all stakeholders will help better
address diabetes.
The literature review has established diabetes as a complex and multifaceted case.
The design needs of this qualitative study were best served by the case study research
approach. The main case of this study was the challenge posed by diabetes, and the
proposed solution was to examine the practicability and challenges of using an integrative
approach to address the emerging diabetes pandemic in India.
This chapter includes the rationale for the chosen case study research design; the
role of the researcher; the methodology followed; the choice of instrumentation; the
schematic design and steps involved in the study; the process and procedure for
recruitment, selection, and participation for data collection; and the data analysis plan.
The chapter ends with a review of trustworthiness and ethical procedures that were
followed in this study, as well as a summary and conclusions.

70
Research Design and Rationale
A robust research design paves the way for sound rationale and methodology for
scholarly research. Any weakness in the design or rationale makes the study and its
conclusions and findings vulnerable. The research questions identified for this study to
understand the rationale for the research design plan were as follows:
1. How can the modern and traditional medicine approaches be jointly deployed
to contain the spread, scale, and immensity of the emerging diabetes pandemic
in India?
2. What are the challenges and barriers of combining the methodologies
propounded by traditional systems (AYUSH) with those of modern medicine
in containing diabetes?
The research questions chosen for this study were evaluated using the qualitative
research methodology. The qualitative method provided the framework to understand the
specific needs of this project. The qualitative design was the most appropriate for
answering the research questions of this dissertation. The above research questions were
investigated through in-depth participative engagement with important stakeholders.
Quantitative and mixed methods were not as appropriate for this study because the goal
of this study was not numerical analysis but an insightful analysis of how modern and
complementary health traditions could be deployed in an integrative manner for
addressing the health priorities and needs arising out of the emerging diabetes pandemic.
The study aimed to evaluate subjective views on the quality of human experiences.
Qualitative procedures rely on text and image data (Creswell, 2003), which are more

71
relevant than mere numerical data. A qualitative approach helps researchers understand
the human and behavioral factors for health conditions and seek views of the community
to initiate action for change (Creswell, 2003).
After evaluating all five major approaches to qualitative research—namely, case
studies, narrative research, phenomenology, grounded theory, and ethnography—I chose
case study as most appropriate approach for my qualitative research. Case study involves
exploring an issue through “in depth data collection using multiple sources of
information” (Creswell, 2007, p. 73). The study was an intrinsic case study design
evaluating the case for using an integrative approach to address the challenges posed by
the emerging diabetes pandemic in India.
Role of the Researcher
Maxwell (2005) summarized the role of the researcher as follows:
Qualitative researchers typically study a relatively small number of individuals or
situations and preserve the individuality of each of these in their analyses, rather
than collecting data from large samples and aggregating the data across
individuals or situations. Thus, they are able to understand how events, actions,
and meanings are shaped by the unique circumstances in which these occur. (p.
221)
In my role as a researcher, to understand and explore the case for diabetes and for
a new approach to addressing the rising incidence and growth of diabetes, I observed and
interviewed the participants of the study in an objective manner. The participants were
invited to be a part of this study after their due acceptance. They did so consensually and

72
in the place and time of their own choice. As the participants were selected through an
objective process and were not related to me in any way, I did not experience any
situation of conflict of interest. I ensured that the process of interviewing was unbiased to
the best of my ability. The study was conducted and analyzed without any prejudgment
or preconception. I analyzed and stored the collected data and identified patterns and
themes using the coding method.
Methodology
Qualitative research involves intense personal interaction between the researcher
and participants. The choice of sample size was crucial. Theorists assert that the success
of qualitative research depends upon the choice of method and criteria used in
determining the type and size of sample. There are many different approaches and criteria
used by researchers to select a purposeful and information-rich sample and to determine
the size of the sample in qualitative research (Patton, 2002). Quantitative research
methodology uses the statistical theory of random probability sampling for sample size to
be seen as representative of the chosen population. A scientifically designed sampling
approach is possibly the most distinctive point of differentiation between quantitative and
qualitative research. Sampling is equally critical in the qualitative and quantitative
methods. The rationale for my choice of sampling methodology is reviewed in this
portion of the study. Referring to qualitative sampling, Patton (2002) used the expression
purposeful sampling. The choice of sample has to be purposeful and information rich
(Patton, 2002).
The case study approach uses six common sources of evidence (Yin, 2009): (a)

73
direct observations of the researcher; (b) data from interviews or open-ended
conversations with key participants; (c) relevant archival records; (d) published
documents such as newspapers, articles, letters, blogs, emails, and reports; (e) indirect
observations of the participants; and (f) physical artifacts and objects related to the theme
of the research (Yin, 2009). For the subject of my research, I used observations,
interviews, archival records, and other published documents.
The research problem in this dissertation was addressed by using the combination
or mixed purposeful sampling approach. The two key components of this approach are a
stratified purposeful sampling approach and a snowball or chain sampling approach. The
rationale for stratified sampling was that there was a need to interview practitioners of
both modern and traditional medicines and policy planners to get meaningful answers to
the research questions. To get the most insightful views from the physicians in the
respective fields, I purposefully identified appropriate representative stakeholders from
each identified stream of medicine using the databases of the regulatory agencies
(explained later in this chapter). Against the chosen framework of purposeful sampling,
the more commonly used random sample framework was not appropriate for this study.
The snowball or chain sampling approach was relevant, as the interviewed participants
kept referring discussions to their peer practitioners, who might provide additional
perspective. The sampling process used is depicted diagrammatically in Figure 10.
74
Figure 10. Sampling process.
Procedures for Recruitment and Data Collection
The sampling process was a combination of the stratified purposeful and
snowballing processes. I interviewed 36 experts to seek answers to the research
questions: five from modern medicine, five practitioners from the Ayurveda school of
traditional medicine, five practitioners from the Unani school of traditional medicine, five
practitioners from the Siddha school of traditional medicine, five practitioners from yoga
and naturopathy, five from homeopathy, and six public health policy planners and health
administrators.
The desired sample of participants was randomly selected from the database of
the nodal research agencies of modern and traditional medicine in India. The accessed
databases were from the records of the Indian Council of Medical Research
(www.icmr.nic.in), the Central Council for Research in Ayurvedic Sciences
(www.ccras.nic.in), the Central Research Council of Siddha (crisiddha.tn.nic.in), the

75
Central Research Council of Unani Medicine (http://www.ccrum.net), the Central
Council for Research in Homeopathy (www.ccrhindia.org), and the Central Council for
Research in Yoga and Naturopathy (http://www.ccryn.org). I explained the objective of
this research and the research questions and asked the respective Councils for approval to
access their public access database for random selection of 15 names of physicians and/or
practitioners from each stream of medicine. Of the 15 chosen names from each stream of
medicine, letters of invitation to participate were sent to a random five. The process
resulted in the selection of the names of 30 participants from the medical community.
There were five each from modern medicine, Ayurveda, Siddha, Unani, yoga and
naturopathy, and homeopathy. Purposeful sampling is a strategy in which particular
settings, persons, or events are deliberately selected for the important information they
can provide that cannot be gotten as well from other choices. Purposeful sampling is used
to capture the heterogeneity in a population (Maxwell, 2005). The 36 participants
interviewed in this study were medical professionals and public health policy planners of
good standing and reputation. I had no professional or personal relationship with any of
the experts. I did not influence the beliefs or responses of any participant in any way. The
process was objective and ethical in all respects.
The research process was fair and objective, and there were no issues or ethical
concerns arising out of it. My work environment and personal contacts had no role to
play in the selection process of the participants. Collecting information and data from a
diverse range of individuals and settings using a variety of methods and diligent
documentation reduced the risk of bias. Through detailed interviews, I collected the data

76
that helped in understanding the views of all participants. Recording the interviews
and/or taking detailed notes and then transcribing the interviews verbatim ensured the
validity of the study.
Using the database of the nodal research councils provided me with the targeted
15 physicians and practitioners for this study. For recruiting public health policy
planners, I reached out to the Health Secretary of the Indian Government to access names
of officials and planners who were in positions of responsibility to contribute to this study
as participants. Against the minimum planned number of five policy administrators/
planners, I interviewed six to ensure compliance with the saturation norm of data. The
sixth name came up as a result of a snowballing process.
After the names were obtained from the nodal research councils and other
indicated authorities, the potential participants were contacted by phone and mail. They
were then provided with the entire background of the research, and the objectives of the
interviews were explained in detail. The potential participants were requested to confirm
their acceptance to participate. I met with the willing participants to obtain their
signatures on the consent form (as per WHO template and guidelines and as approved by
Walden University IRB, attached as Appendix I). Each interview was conducted at a
place and time convenient to the participant. All 36 interviews were conducted
individually and not in a group. The interviews were audio recorded whenever approved
by the participants. In other cases, detailed notes were taken during the interviewing
process. A letter of thanks and gratitude was given following the interview. All
transcribed data were securely stored for confidential research use. All transcripts and

77
recordings were carefully reviewed in their entirety, and data were coded using Microsoft
Word software. The composition of the 36 participants is depicted in Figure 11. The
figure includes sub classifications of participants in the fields of modern medicine, yoga
and naturopathy, and policy.
Figure 11. Composition of participants.
The process flow chart used for the qualitative research of this study is shown in
Figure 12. The process of research started with detailed interviews with chosen
constituents. As the sole researcher conducting these interviews, I also observed the
workplace of all practitioners and made notes on other observed attributes.
F !physicians!
!modern!
!
Three!!General!
Physicians!
Two
endocrinologists
F !physicians!
!Ayurveda!
F !physicians!
!Yoga!and!
N !
Three!from!Yoga! Two!from!
Naturopathy!
F !physicians!
!Unani!
F !physicians!
!Siddha!
F !physicians!
!
H !
Six!Policy!
Planners/
Administrators!
Two!from!
Regulatory!
Agencies!
Two!from!Federal!
Government!
One!from!State!
Governments!
One!
administrator!
from!private!
sector!
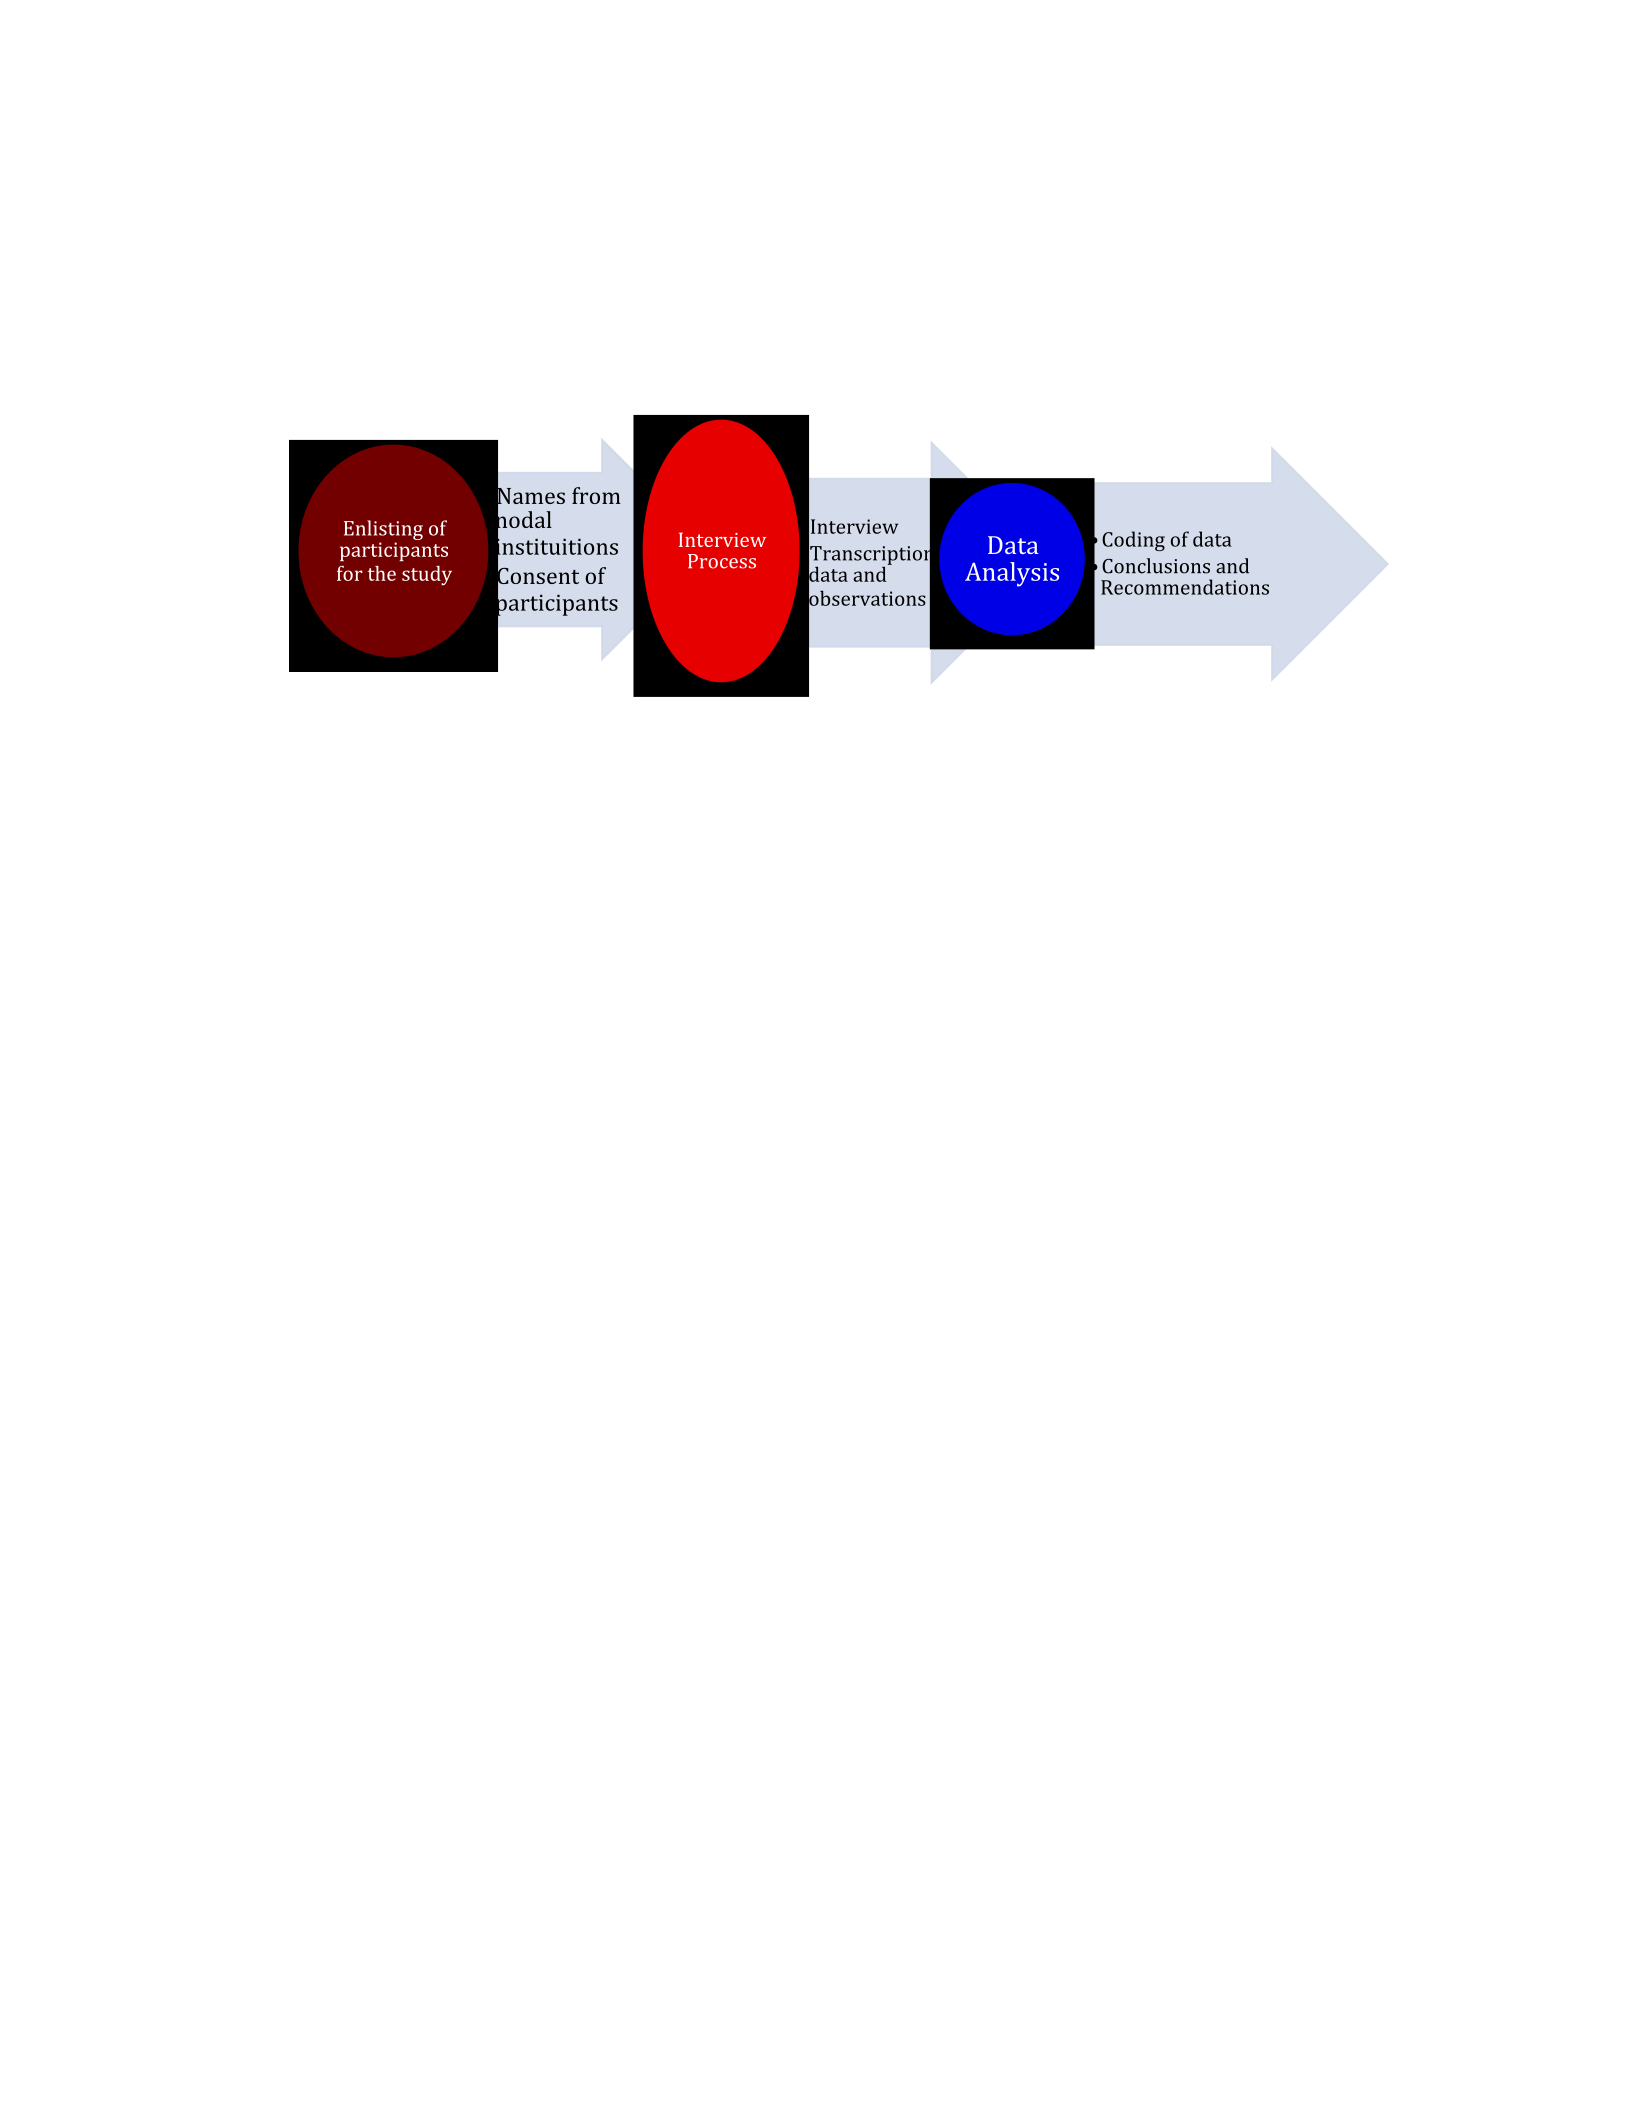
78
Figure 12. Flow chart of process.
The questionnaire that was used for the interviews is attached in Appendix 1.
Though Hindi translation of the questionnaire (attached as Appendix B) was available in
accordance with the IRB approval process, it was not used, as all participants were
proficient in English. Interviews lasted between 45 and 60 minutes. Where permitted,
these were audio-recorded with the consent of the practitioner/participant; with others,
detailed notes were taken to ensure that the views of participants were fully captured.
Details of observation were also documented to correlate and triangulate with the
interviews during the analysis of data.
The instruments that were used in this study are detailed below. As I was the sole
interviewer and data analyst for all 36 participants, the study did not require any training
for field researchers or data analysts. I used the three primary instruments in the interview
process. First, I used the interview sheet to record the answers and comments of the
participants; second, I used an observation sheet to record my impressions of the
interview locale and elements such as body language and visual cues from the
• Names!from!
nodal!
instituitions!!
• Consent!of!
participants!
Enlisting!of!
participants!
for!the!study!
• Interview!
• Transcription!of!
data!and!
observations!
Interview!
Process!
• Coding!of!data!
• Conclusions!and!
Recommendations!
Data!
Analysis!

79
participants. Finally, the audio recording of the interview, where available, was
transcribed verbatim. The interview process had three phases. The first phase was the
request letter to the nodal agencies to access the database shown in the above diagram.
The second phase involved communication with the people whose names came up in the
random selection process from the databases. Third, I communicated with the participants
in order to set up times for the interviews and to seek continued engagement in the spirit
of participatory action research.
Snowballing Suggestion of Participant Names
During the interview process, one or more participants suggested inclusion of
another point of view related to the research. As snowballing was an anticipated
possibility, a letter to add snowballing participants, its Hindi translation and back
translation was placed in Appendices L, M, and N.
Data Analysis Plans
Interviews and observations resulted in high volume of data. The analysis of data,
evaluation and interpretation revealed insightful lessons. The purpose of this study was to
assess the practicability of using an integrative approach as a potential solution for
India’s emerging diabetes pandemic. The interview responses were fully transcribed. As
in most qualitative research, data collection and data analysis were done simultaneously.
Transcribing the interviews helped me to acquire a deeper understanding of the views of
participants. Qualitative data from interviews and observations were sorted as per themes
to derive the substantive content. The themes were then coded and analyzed.
Qualitative analysis of text is often supplemented with other sources of
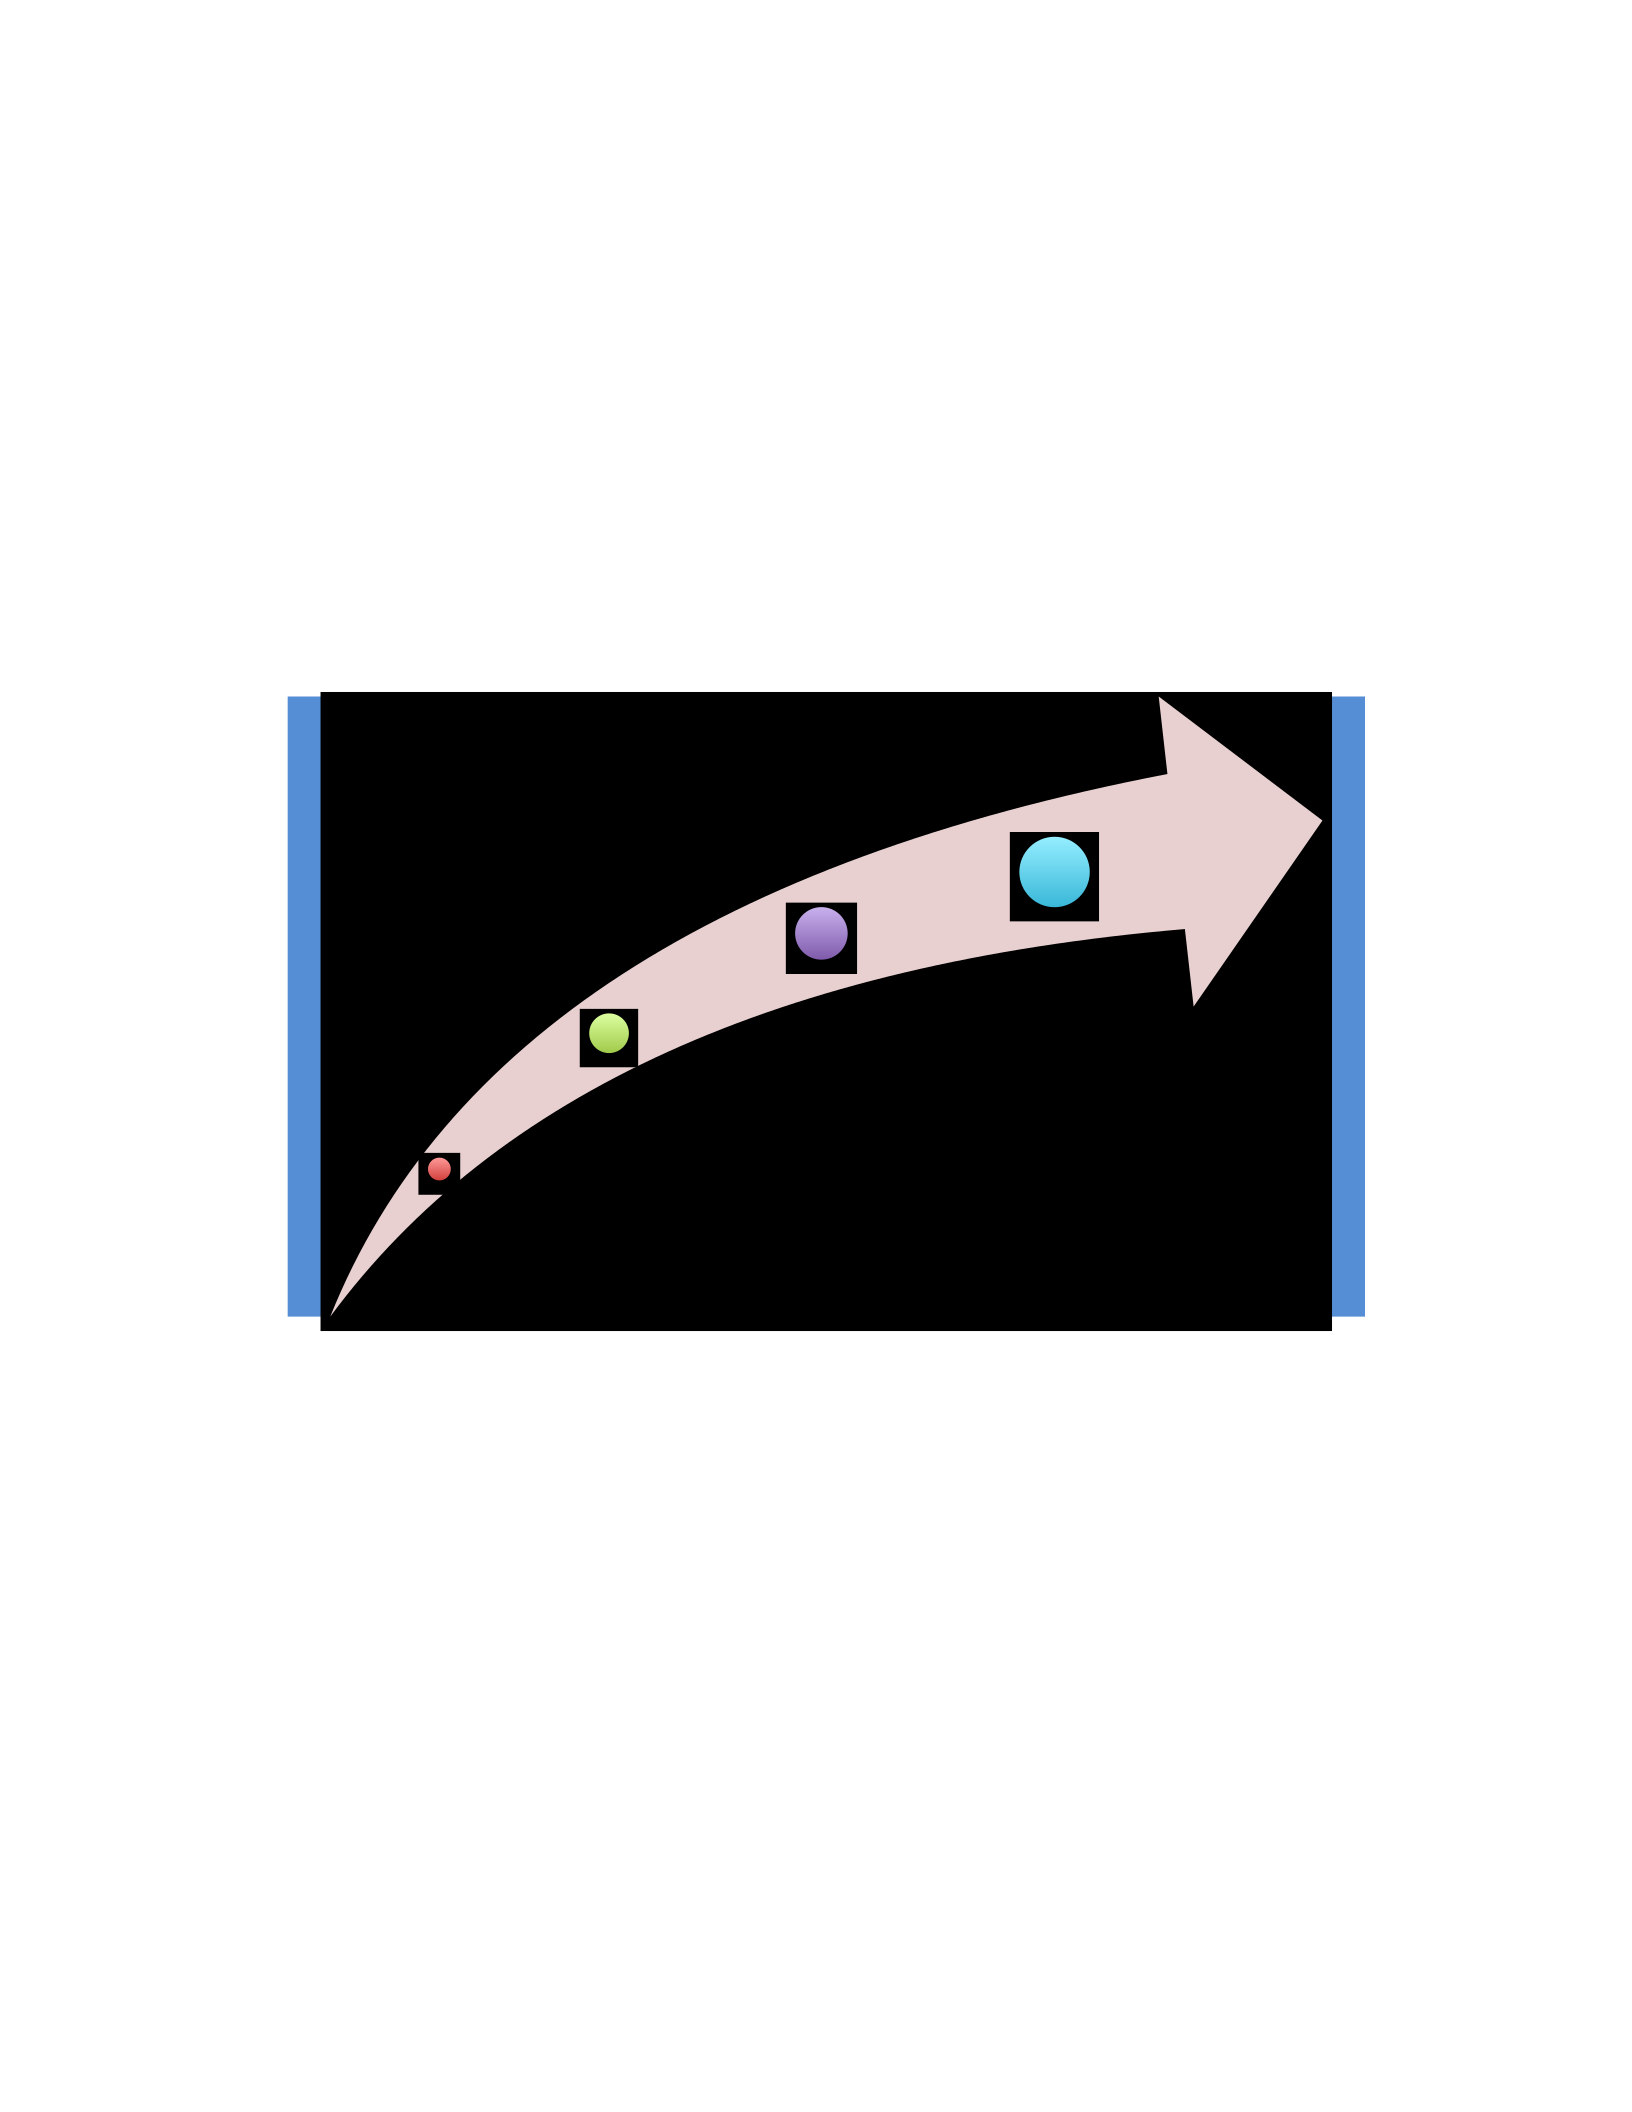
80
information to satisfy the principle of triangulation. Triangulation strengthens study by
combining methods (Patton, 2002). Triangulation increases trust in the validity of the
study’s conclusions. Triangulation was used to analyze the transcribed interviews,
observational field notes and documents authored by the respondents themselves. The
purpose of multiple sources of data is corroboration, converging evidence and to enhance
the validity and credibility of the study.
Figure 13. Data analysis plan.
Issues of Trustworthiness
Any research process has threats to internal and external validity and these must
be addressed to increase the trustworthiness of the research process. Interviews and
observations generated data that was interpreted after insightful evaluation and coding to
derive meaning and essence hidden in the data. The case study of management and
prevention of diabetes was looked at from a new perspective and the findings of the study
Raw!data;!
interview!
notes!and/or!
audio!
recordings!
Transcripts!and!
observation!
notes!
Coding!and!
primary!
analysis!
Analysis!and!
Conclusions!

81
provided meaningful insights only because the trustworthiness was assured.
Credibility
Credibility of qualitative research substantially depends on the researcher, who is
the primary instrument of research (Patton, 2002). I identified three possible threats to
internal validity. The first was the possibility of my being over-passionate about the cause
and harboring a sense of urgency and my disappointment with the state apparatus, which
has the responsibility of delivering the national public health objectives. The second was
the possibility that the proposed research questions would not evoke warmth and the
kind of response that is required to reach meaningful conclusions. The third was that as
sole researcher and data analyzer, my personal biases and prejudices may get transferred
to the study. I was fortunate that none of these three or any other threats impacted the
quality or speed of my work.
To ensure credibility of the study, being aware of the possible threats, helped me
to avoid and circumvent the pitfalls. Observing the participants diligently and conducting
the interviews dispassionately ensured reliability of the study. Observation, interview,
and frequent visits to appropriate settings helped me gather detailed and descriptive data.
The transcribed data were shared with the participants for clarification and to confirm
accuracy of transcription and fortify credibility of the research and transcription process.
No external threats were encountered. The external threats potentially could have come
from the regulatory side of policy administrators who may have discouraged any form of
collaboration between the modern and traditional systems of medicine. There are some
people who may look down upon the other medical systems because of their own

82
misgivings and misapprehensions and may have the ability to influence the quality of
data by their pronouncements and diktats. In my experience, I did not come across any
such external resistance in conducting this research.
Transferability
The transferability of the study and its findings to related contexts and research
situations was important and reflected the strength of design, assumptions and the
process. Transferability was made possible by providing exhaustive details and specifics
of the assumptions, sampling strategy and the thought process followed to determine the
research design of the study. The study had clearly spelt out the constraints and
limitations met during the process of collection and analysis of data. Providing these
details will make it easier for any researcher or reviewer to seek transferability of this
study. The phenomenon of diabetes is global and the scale and enormity of challenge
merits wide collaborations and corroboration between and among researchers. A sound
transferability framework will help this cause.
Dependability
The scale and magnitude of challenge posed by diabetes in India and the world is
engaging global attention from the policy planners, global and national institutions,
academic researchers and solution providers. Dependability of the study was ensured by
diligent conformance to the defined protocol and accurate transcription of the collected
data. I made conscious efforts not to allow any preconceived views, notions or prejudices
from impacting the process of study and/or its eventual findings. Along with audio
recordings of the interview and observation, I also kept detailed notes to elaborate in the

83
study process. Clear focus on the research questions and observance of research process
as laid out in the design was significantly reinforced to ensure the dependability factor of
the study.
Confirmability
The interviews were audio recorded wherever possible so that all transcripts
accurately captured the responses from the participants. Triangulation, a time tested tool,
was also used to establish confirmability. Triangulation was done by collected data
during the observation process and cross-referencing with the transcripts of interviews
and comments from the peer group during the process of coding and analysis. The
triangulation process also included the data generated during the literature review
process. The collected data from diverse individuals and settings supported the
confirmability factor of the study.
Ethical Procedures
All agreements, approvals and consents were obtained before I approached the
participants to ensure implementation of required ethical procedures. Participants in this
study took part in the interviews on a voluntary and willing basis. Prior consent was
obtained to interview using the WHO consent forms for qualitative studies as enclosed in
Appendix I. The consent forms in Hindi language were also available in Appendix J
(reverse translation in Appendix K) but were not used, as all participants were proficient
in English. The participants were assured of the confidentiality of their responses. The
contents of the interviews were not disclosed to anyone else and the data were used for
research purposes only. In seeking the support of the participants all appropriate

84
approvals and consents were obtained from the people involved.
Protection of Human Participants
The study was undertaken after due approval by the Institutional Review Board of
the Walden University (IRB approval # 04-21-14-0191600). Only publically available
documents were used and included in this study. No confidential documents, patient
records or private health information were accessed, used or analyzed in this study.
Summary and Conclusions
In this chapter, the research methodology of the study and the process that was
followed has been reviewed. The rationale of the choices made for the theoretical
constructs; framework, and sampling methodology have been reviewed in detail. The
choices of instrumentation, process of data analyses, and the ethical framework used for
the study have also been reviewed. The steps that were followed were: enlisting the
participants; approaching them for interviews; conducting the interviews, and analyzing
the data to find answers to the research questions outlined for this study. The choice of
participants for the study also included policy administrators. The results of research have
been detailed in the next chapter.

85
Chapter 4: Results
Introduction
All participants in the study endorsed an integrative approach as a practical and
feasible solution to the emerging pandemic of diabetes in India. Exhaustive analysis of
data generated in interviews and observations revealed that both the medical practitioners
and the policy administrators supported the research proposition of an integrative
approach as a possible solution for managing diabetes. The detailed process of data
collection used in this research and the process followed for analyses of results and the
research findings have been explained in this chapter.
The purpose of this study was to assess the practicability of using an integrative
approach as a potential solution to India’s emerging diabetes pandemic. The research
questions for which answers were sought using the five-question questionnaire were as
follows:
1. How can the modern and traditional medicine approaches be combined to
contain the proliferation and immensity of the emerging diabetes pandemic in
India?
2. What are the challenges and barriers of combining the methodologies
articulated in the traditional systems (AYUSH) and the modern system of
medicine in containing diabetes?
Before interviewing the participants, I researched peer-reviewed journals to
understand the key aspects of all the traditional forms of medicine followed in India and
the current policy framework on practice norms of AYUSH in different states of India. I

86
read over 108 journal articles and looked through several books to understand the major
challenges posed by diabetes and the significant themes that literature had covered. This
prepared me well for conducting interviews and collecting data to answer my research
questions.
The answers to the two research questions were sought through 36 in-depth and
structured interviews. The following five questions were asked to each of the 36
participants:
Q1. What are the main guidelines in your medical tradition that might help
prevent occurrence of diabetes among Indians in the age group of 25-45
years?
Q2. Please list five important preventive actions, as stated in your system of
medicine, by practicing which a person can minimize the risk of becoming
diabetic?
Q3. What are your views on the coexistence and concurrent usage of your medical
tradition with other medical traditions in India, that may help address the
emerging epidemic-scale challenge of diabetes in India?
Q4. What, in your assessment, will be the main challenges of combining the
modern and traditional schools of medicine to tackle the rapidly growing
incidence of diabetes in India?
Q5. What are the policy changes that would be required to check the incidence of
diabetes in India?

87
The 36 interviews were carried out between 24 April 2014 and 6 July 2014 over a
period of 74 days. The later part of this chapter describes the setting, the demographics of
participants, the data collection process, and the instruments used, the data analysis, and
the process used to derive codes and themes. The chapter closes with evidence of
trustworthiness of the data collection and the steps and process followed for the analysis
of data.
Setting
All interviews were conducted after due consent of participants and at times and
places convenient to the participants. The interviews were all conducted at the clinics of
medical practitioners and offices of policy planners/administrators. Visiting the
practitioners’ clinics gave me the chance to observe their settings closely and understand
the dynamics of patient-physician interaction and how typical patients spent their time
while waiting for their turn to see the physician. I noted what I observed, and these data
were used as a source of triangulation to validate the findings. I also made note of the
posters, public health messages, and medical materials displayed or kept as leaflets at the
clinics and the offices of policy planners/administrators.
Demographics of Participants
The names of 30 out of the 36 participants were obtained from the database of
registered practitioners maintained by the Central Research Councils of Modern
Medicine, Ayurveda, Unani, Siddha, and Yoga and Homeopathy, as envisaged in the
design of the study. Five names of policy planners were obtained from the database of
policy planners and administrators maintained by the federal and state governments. In

88
the design of the study detailed in Chapter 3, the plan was to obtain 15 names from all
databases to provide cushion for nonavailability of people or disinclination of shortlisted
participants to join and/or participate in the study. While I had list of 15 randomly chosen
names from each medical tradition and policy planners/administrators, the first five
randomly chosen participants in each category agreed to join this study and signed
consent forms prior to interviews.
In the case of policy planners and administrators, I had to go beyond the
minimum planned number of five participants, as data saturation was not fully achieved
after conducting interviews with five policy planners/administrators. The sixth name
from the category of policy planners came out of the snowballing process. The policy
administrators in the government sector reminded me that nearly 75% of India’s
healthcare delivery takes place in the private sector and that it would be important to have
views and inputs from a health administrator in the private sector. The sixth administrator
interviewed as a result of the snowballing process was an administrator from the private
sector. The additional interview also helped to reaffirm and meet the data saturation test.
In accordance with the approval of Walden University IRB, I had prepared Hindi
language versions and back translations of the interview questionnaires and forms for
informed consent and other important communications to be ready for a situation where
any participant showed a preference to use the Indian national language, Hindi, over
English. It turned out that all 36 participants were proficient in the English language, and
as a result, the Hindi-language versions of questionnaires and consent forms were not
used. The availability of Hindi language materials was conveyed to all participants. The

89
translated versions in Hindi and back-translated versions of the questionnaire, form for
informed consent, and letter of invitation for snowballed participation have been placed
as appendices at the end of this dissertation. The contribution of two professionals who
helped with the translations and back translations was duly acknowledged.
Data Collection
The data collection was done through interview sheets and audio recordings. Of
36 participants, 10 agreed to allow audio recording of interviews. The other participants
declined approval for audio recording and asked me to make elaborate notes to capture
their answers. The voice files of interviews that were audio recorded were transferred
from the voice recorder of my iPhone to the hard disk of my computer with password
protection. Detailed interview notes were tallied and confirmed with responses to all
questions at the conclusion of the interview to ensure that all information was correctly
captured. The handwritten interview notes and observation comments were transcribed
on the computer using Microsoft Word for Mac software. The observation notes in all
cases corroborated the answers given by the participants.
90
Figure 14. Number of interviews, audio recorded and hand noted.
Number of Participants
Thirty-six participants were interviewed for this study. Of the 36 participants, 30
were medical professionals (five each from modern medicine and the five branches of
AYUSH). In the case of modern medicine, yoga and naturopathy and policy
planners/administrators, there were further subdivisions. The modern medicine stream
had three general/family physicians and two endocrinologists, as diabetes falls in the
endocrinology subspecialty. The yoga and naturopathy stream had three yoga
practitioners and two naturopaths. Of the six participants from the category of policy
planners/administrators, there were three federal policy planners/administrators, two from
the states and one from the private sector. The composition of the 36 participants is
captured in Figure 15.
10!
26!
Number!of!interviews!
that!were!audio!
recorded!
Number!of!interviews!
that!were!hand!noted!
91
Figure 15. Composition of 36 participants.
Data Analysis
Data from all 36 interviews were transcribed using Microsoft Word software on a
MacBook Pro laptop computer. The data files were backed up on a separate hard drive.
Both the original and backup files were password protected to ensure data security as
stated in the design of the study. The data were analyzed in a five-step process to move
inductively from raw data to codes and from codes to larger representations of categories
and themes. The five-step data analysis process started with careful first reading of raw
transcribed data from all 36 interviews. In the second stage, the key words, expressions,
and statements from all interviews were hand coded. In the third stage, the data were
machine coded to derive key words, themes, statements, and expressions. In the fourth
stage, the hand-coded and machine-coded data sets were compared to derive the themes
0!
1!
2!
3!
4!
5!
6!
7!
Modern!Medicine!
!V!General!Physicians!
V!!Endocrinologists!
Ayurveda!
Siddha!
Unani!
Yoga!&!Naturopathy!
V!Yoga!
V!Naturopathy!
Homeopathy!
Policy!Planners/
V!Federal!
V!State!
V!Private!
Number'of'participants'
Number!of!participants!
92
and categories induced from the two processes. At this stage, the data were also reviewed
to analyze differences and dissents to identify discrepant notes. In the final stage of data
analysis, the conclusions were derived alongside recommendations and leads for further
research.
The above five-stage process is explained in Figure 16 on page 92. The actions
associated with each step of data analyses have also been depicted in Figure 16 on page
92.
Figure 16. Five-stage process of data analysis.
Codes and Categories
A number of important themes and concepts emerged from the process of data
analysis and inductive coding. Both open and axial coding processes were used for data
analysis. These codes and themes were first summarized under each question and later
clustered into themes and thematic conclusions in response to the two research questions.
R !Data! • Transcribed!
H !
C !
• Key!words,!
codes,!themes,!
statements!
M !
C !
• Key!words,!themes,!
statements!
C !&!
A !
• Codes,!themes,!
discrepants!
R
,!
C !
• Strategic!
Insights!

93
The views on two research questions were taken using the five-question questionnaire,
which was common to all categories of respondents. The codes that emerged from the
analysis of data are summarized below in tabular form. The induction of themes and
categories that emerged from these codes is also summarized in Table 1. The codes are
listed in the left column, and the corresponding themes are in the right column in Table 1.
Table 1
Codes and Themes Derived From Data
Theme
Codes
Desirable
Desirable
Possible
Feasible
Great idea
Worthy of evaluation
Timely
Much needed
Preventative
Diet
Fitness
Health monitoring
Moderation
Balance
Avoidance of stress
Prevention
Prophylactic
Exercise
Regularity
Discipline
Detox
Raw foods
Modification
Regular yoga
Breathing
Relaxation
Five elements
Prophylactic herbs
Plants
Herbs
Minerals
Coexistence
Regular testing
Stimulate pancreas
Fat metabolism
Magnesium
Vitamin B6
Policy concerns/challenges
No regulatory focus
Attention
Prudence
Patient-centric approach
Worthy of evaluation
Common acceptable protocol

94
Theme
Codes
Absence of prior experience
Skilled AYUSH practitioners
Quackery
Pharmacological risks
Consequences beyond diabetes into other disease areas
Health as a state subject
Enforcement issues
Limited experience
Enabling
Medicines
Education-awareness
Comorbidities
Obesity
Foot examination
Mass education
Awareness
Mass media
Mass media deployment
Mobile telephony
Text messaging
Future of integrative approach
Pharmacological commonalities
Pathway studies
Clinical trials
Yoga coexistence
Better absorption
Meeting point of diagnostics
Adjunct therapy
Complementary therapy
Implementation
Robust oversight mechanism
Potential misuse
Mandatory Screening
Mandatory screening
Patient-centric approach
Path forward
Doctors to discuss diabetes with all patients
Educational materials
Greater recognition for AYUSH
Stricter quality standards
Complementary traditional medicines
Medical protocol
Insurance reimbursements for AYUSH
Yoga on national television
Funding for clinical research
Validation studies
National school of integrative health
Leverage key learnings from all traditions
Comparable weightage to modern medicine and AYUSH
Synchronous priorities of research—both modern medicine and AYUSH
Standard operating procedures
Alternatives for treatments
Model institutions
Pilot centers
Complementary therapy
Incentives
Discrepant codes/themes
Naturopathy’s non acceptance of chemicals
Self-trained homeopathy
Large regulatory scale
Resistance from practitioners of modern medicine
Non compatibilities

95
Key Themes
Seven key themes emerged from detailed review and analysis of data and the
coding process. The seven themes captured the essence of codes and themes summarized
in table 1. These themes were:
• Integrative approach is a desirable solution for managing the challenge of
diabetes.
• Every medical tradition has preventative tools and suggestions for avoidance
and management of diabetes. These can be widely publicized and deployed to
contain the proliferation of diabetes.
• There are policy concerns and challenges for implementing integrative
approach that would need to be addressed for rolling out the integrative
approach.
• Public education and greater awareness of integrative approach can help
improve preparedness to meet the challenge of emerging diabetes pandemic.
• Integrative approach has the potential to open up avenues and possibilities for
further research to meet the challenge of diabetes.
• Specific steps and guidelines will be needed to help effective implementation
of integrative approach.
• Lastly the path forward for implementing integrative approach in terms of
suggestions and actions required institutionalizing integrative approach.
The process of transition from research questions to the interview questions and
the emergence of themes from the codes are explained in figure 16 on page 97. Figure 16
96
on page 97 maps the movement from two research questions to five interview questions
and the seven themes from analyses of data, relating them back to the two research
questions.
Research Questions->-> Interview Questions->-> Analyzed Themes
Figure 17. Transition from research questions to interview questions and from questions
to the themes clustered from codes.
How!can!the!modern!and!traditional!
medicine!approaches!be!combined!to!
contain!the!proliferation!and!
immensity!of!the!emerging!diabetes!
pandemic!in!India?!
What!are!the!main!guidelines!in!your!
medical!tradition!that!might!help!
prevent!occurrence!of!diabetes!among!
Indians!in!the!age!group!of!25V45!
years?!
Integrative!approach!is!a!desirable!
solution!for!managing!the!challenge!of!
diabetes.!
Every!medical!tradition!has!
preventative!tools!and!suggestions!for!
avoidance!and!management!of!
diabetes.!These!can!be!widely!
publicized!and!used!to!contain!the!
proliferation!of!diabetes.!
Please!list!^ive!important!preventive!
actions!as!stated!in!your!system!of!
medicine,!by!
practicing!which!a!person!can!
minimize!the!risk!of!becoming!
diabetic?!
Public!education!and!greater!
awareness!of!integrative!approach!can!
help!improve!preparedness!to!meet!the!
challenge!of!emerging!diabetes!
pandemic.!
Request!your!views!on!coexistence!and!
concurrent!usage!of!your!medical!
tradition!with!other!medical!traditions!
in!India,!that!may!help!address!the!
emerging!epidemic!scale!
challenge!of!diabetes!in!India?!
Integrative!approach!has!the!potential!
to!open!up!avenues!and!possibilities!for!
further!research!to!meet!the!challenge!
of!diabetes.!
What!are!the!challenges!and!barriers!of!
combining!the!methodologies!
articulated!in!the!traditional!systems!
AYUSH!and!the!modern!system!of!
medicine!in!containing!!
diabetes?!
What!in!your!assessment!will!be!the!
main!challenges!of!combining!the!
modern!and!
traditional!schools!of!medicine!to!
tackle!the!rapidly!growing!incidence!of!
diabetes!in!India?!
There!are!policy!concerns!and!
challenges!for!implementing!
integrative!approach!that!would!need!
to!be!addressed!for!rolling!out!the!
integrative!approach.!
What!are!the!policy!changes!that!would!
be!required!to!check!the!incidence!of!
diabetes!in!India?!
The!path!forward!for!implementing!
integrative!approach!in!terms!of!
suggestions!and!actions!required!
institutionalizing!integrative!approach!
Speci^ic!steps!and!guidelines!will!be!
needed!to!help!effective!
implementation!of!integrative!
approach!

97
A commentary on the seven themes listed above along with a few vignettes
follows:
Theme 1: Integrative approach—Desirable. The first theme was that the
proposed integrative approach of combining modern medicine with AYUSH traditions to
address the challenge of emerging diabetes pandemic was feasible, desirable, and much
needed. The participants commented on the subject of dissertation as both being
“desirable and opportune in terms of timing,” given the “scale of proliferation of
disease.” The comment from one participant was very pertinent. “By doubling the
available medical pool by combining doctors from modern medicine and AYUSH, India
will be much better equipped to face the challenge of diabetes. “This is not just desirable
but an absolute necessity.” One participant remarked, “If our existing method and
strategy were effective, we will not be seeing such high growth numbers of people with
diabetes.”
Vignette 1
Gita was six months pregnant and lived in a remote village. She had to change two buses and then walk for
three kilometers to access the nearest hospital. She arrived at the hospital thirsty and tired and had to
patiently wait for her turn to see the specialist. Since she had to be empty stomach for the blood tests, she
had to control her pangs of hunger till she completed the diagnostic investigation. The Ayurveda doctor
Gita consulted in the village suspected Gita had diabetes but wanted a confirmatory test that was
unavailable in the remote village.
Theme 2: Integrative approach—Preventative tools. The second theme was
that an integrative model that combines modern and traditional medicines would make it
possible to have many more preventative tools that could be popularized. By using these
preventative tools, people can avert onset of diabetes and also have access to tools and
98
methods for better management of disease where a patient had already developed
diabetes. The interviews provided useful data and information on preventative methods in
different medical traditions to prevent and/or contain diabetes. Two pertinent comments
from participants brought out the importance of preventative tools. “As doctors, we know
that diabetes is preventable. All it needs is an active lifestyle and prudent diet. The
guidelines in modern medicine and traditional systems will offer a wide choice of
preventative tips that can be used both by high-risk individuals.” The second comment
related to importance of prevention. “Prevention is better than cure is well known and is
worth every effort to avert a chronic health condition like diabetes. The wider choice of
preventative tools will improve chances of prevention for many families.”
Vignette 2
Living alone, Sajid had to manage both his work and home. Since he worked at a call center, his diet and
schedule could never get streamlined. He had to work at odd hours, eat whatever and whenever he could
grab. He had no time to organize a fresh healthy meal. His pre-diabetes unfortunately degenerated into
diabetes because of his own negligence.
Theme 3: Integrative approach—Challenges. The integrative approach of
combining modern medicine and AYUSH had a few important challenges that needed to
be addressed. The integrative approach also had potential for some areas of misuse and
abuse. The challenges arose from some inherent contradictions among various medical
traditions as to how the disease could be treated. One of the participants stated, “AYUSH
traditions give significant role to diet and lifestyle and some of the constituent systems of
AYUSH like naturopathy do not accept a role for chemically prepared medicines.”
Participants, particularly the policy planners were also concerned that some of the self-
99
anointed non-qualified AYUSH practitioners could use this as an opportunity to enter
mainstream of healthcare delivery. The specific comment was very pertinent. “It is
therefore important that integrative model of modern medicine and AYUSH should be
restricted only for those medical professionals who are trained, qualified and licensed to
practice.” Another comment was by way of a suggestion. “The research councils of
modern medicine and AYUSH could synergize efforts for joint research and validation.”
One participant also commented on challenge of “availability of modern and traditional
medicines in pharmacy outlets.”
Vignette 3
Rajni rarely used any medicines and was quite particular and disciplined about her diet and fitness.
Whenever she was unwell she went to her neighbor who practiced homeopathy as a hobby. Her
prescriptions worked well to settle Rajni’s seasonal ailments. This summer however when Rajni
experienced tedium and sudden weight loss she returned to her neighbor for advice. The self-trained
homeopath gave her some pills. Unfortunately, the prescribed medicine caused severe rashes all over
Rajni’s body.
Theme 4: Integrative approach—Awareness/education. The theme that
emerged was that the integrative approach of modern medicine and AYUSH would help
add to the body of knowledge and materials for enhancing public education and
awareness. For the integrative model to be successful, participants favored using mass
media for creating greater awareness. A comment from one of the participants on this
was, “ it should be mandatory for all sporting telecasts and soaps to carry public health
messages on importance of preventing diabetes.” Some of the participants commented
on the possibility of using 900 million mobile telephones in India for sending public
health text messages on diabetes and the integrative model. One of the specific comments
100
was, “nearly every adult in India has a mobile phone. The telecom regulators ought to be
persuaded to allow free of cost public health text messages to build greater awareness of
prevention.” One participant stated that “electronic media has huge influence on all age
groups of people and themes of prevention based on integrative approach could be used
for creating content for all age groups of people including the teenagers and young
adults.”
Vignette 4
David moved form his village to the city to earn more money. He had to stand for long hours at the factory
floor working as a supervisor. His feet would often pain by the end of the day. One day the pain was more
than normal. David noticed an injury on the big toe of his left foot. He did some self-medication and forgot
about it. He had excruciating pain the next week and he could not manage to walk about on the factory
floor. When he finally saw a doctor it was already too late. His toe had to be amputated. David was sadly
unaware of his advanced stage of diabetes.
Theme 5: Integrative approach—Future. The next theme was that an
integrative approach seeking to combine modern and traditional medicine may open up
new frontiers of research on diabetes and other health conditions where best practices and
learning’s from modern medicine and AYUSH could be synergistically used. The
participants commented that the experiment of diabetes could be extended and expanded
to other non-communicable disease as well. The specific comments were: “The non-
communicable diseases (NCDs) like diabetes account for 63% of deaths in India. NCDs
are man-made and can be so redressed. The integrative approach may open new pathways
for joint clinical research to leverage what is best in both the modern and traditional
medicine.” “Continued research is backbone of medical sciences. The useful experiment
of combining modern and traditional medical sciences should encourage Indian
101
Government to fund join research studies.” One of the medical practitioners commented,
“it would help for practitioners to understand salient features of other medical traditions
to offer the best possible solutions to the patients.”
Vignette 5
As a medical oncologist, Dr. Dewan was deeply concerned to see his patients suffer. He was always
looking for complementary and alternative ways of healing to soften the pain of chemotherapy. He was
taking a course in herbal nutrition to understand the mechanics of food and naturopathy in helping with
problems of malignancy. He just wanted his patients to feel better.
Theme 6: Integrative approach—Implementation. It emerged from analysis of
data that a few important policy and regulatory changes would be required to create an
enabling regulatory environment in order to ensure enduring long-term success of
integrative approach. The regulatory framework, participants observed, would have to be
suitably modified to provide parity for modern medicine and AYUSH for insurance
reimbursement and many other steps. Three specific comments emphasized this theme.
One comment was: “ The modern medicine and traditional medicine systems are so used
to working independently of each other that it would need an enabling regulatory
environment and framework to make the integrative model work.” Another comment
was: “The health insurance in India does not reach many people but even where it
reaches, it excludes AUSH treatments from its ambit. The insurance framework would
need to be amended to provide parity for modern and traditional systems of medicine.” A
participant added: “Integrative model of modern and traditional medicine would be useful
to meet the challenge of diabetes but would need support of the regulatory and policy
framework.”
102
Vignette 6
A siddha doctor was preparing for his talk on the principles of siddha medicine. He was the guest speaker
at the world congress of physicians. Everyone was eager to listen to his success story in successfully
treating autoimmune disease. He had worked jointly with physicians from other streams of medicine to
validate his studies. Joint clinical trials were done on all the formulations he had used to test their efficacy.
Diabetes was the next chronic condition this practitioner is working on.
Theme 7: Integrative approach—Path forward. The next theme related to
specific steps that would be required to ensure success of integrative approach. “The
integrative approach could encourage doctors of both modern medicine and AYUSH
stream to initiate a dialog on diabetes every time a patient saw them.” The suggestion
from the participants was that “regulatory authorities could develop standard operating
procedures that could make discussion on diabetes with all patients mandatory.” It was
felt that this “would increase levels of detection of diabetes in India and also prevent
disease burden of many potential or confirmed prediabetics.”
The participants commented that “integrative model of modern medicine and
AYUSH should encourage mandatory screening of all patients for diabetes with
appropriate guidance on lifestyle corrections, exercise and fitness.” A comment offered
by a policy administrator participant was very relevant: “ even a good idea can be
destroyed by poor planning and execution. It is therefore equally important, if not more,
to plan well and execute correctly.” A few other participants sounded this note of caution
as well.
103
Vignette 7
The newly designed integrative health center inaugurated by the minister was a front-runner towards
implementation of integrative approach of healthcare. At the center, all physicians were appropriately
skilled in their respective fields. The patients had a choice to seek treatment in the medical tradition of their
choice. All doctors, both modern and traditional at the center get together every evening to jointly discuss
the health conditions, medical needs of patients and treatment protocols. The approach at the center was
patient centric so that the patients would get the best possible integrative treatment.
Discrepant Cases
The data collection process generated 180 detailed answers. Each of the 36
participants answered five questions from the interview questionnaire. Of the 180
responses, there were three discrepant comments that were worthy of notice and analysis.
The first comment was that “homeopathy is practiced in India by a large number of
people, many who are trained and qualified and others who are self-trained but not
qualified. There was an inherent risk of some quackery creeping its way into an
integrative model by participation of self trained but not qualified practitioners.”
The second discrepant case was a comment by a naturopathy physician that their
“branch of medicine had no role for chemically synthesized medicines and therefore had
some intrinsic limitations on compatibility with modern medicine in an integrative
model.” This in turn could mean that the “patients calling on a naturopathy practitioner
may not receive truly integrative guidance.” The third discrepant comment was from a
policy planner who was apprehensive about the “scale of management and regulatory
apparatus required for ensuring success and preventing misuse of an integrative model.”
The concern of this participant was that the “regulatory and coordination responsibility

104
would have to be well conceived and well managed.” The participant said, “ managing
and coordination multiple streams will be an arduous task. Also because of multiplicity of
agencies involved in administration of modern medicine and AYUSH systems of
medicine who will take the final responsibility of the health and well being of the
patient.”
Commentary on Discrepant Cases/Comments
Only 1.66 % of the total responses had discrepant notes/comments. However,
each of the three discrepant comments was relevant and worthy of attention. Detailed
analysis of comments brought out that these comments were more in the nature of
apprehensions that could be mitigated by appropriate solutions and corrective steps. The
comment on risk of abuse by self-taught homeopaths could be addressed by ensuring that
the integrative model works only with trained and qualified physicians from modern and
traditional streams of medicine AYUSH. The comment of naturopathy not accepting any
chemically synthesized medicines could be addressed by recognizing that the integrative
model will only seek to combine compatible best practices while isolating factors of
concern that go against the benefits of an integrative system of medicine.
Naturopathy as a system of medicine has a large number of practices that are
compatible with and would supplement the efficacy and benefits of modern medicine and
prescriptions from other branches of AYUSH. The third discrepant comment related to
practical apprehensions of a policy planner and administrator on the regulatory and
monitoring framework required to handle double the number of practitioners, as both
modern medicine and AYUSH would contribute a matching 750,000 practicing

105
doctors/practitioners each. The improved and enlarged network of physicians from all
streams of medicine would help successfully implement the projected benefits of an
integrative model.
The research brought out that “integrative approach was expected to benefit large
number of diabetics and prediabetics with improved health outcomes.”
Evidence of Trustworthiness
The framework of trustworthiness for this research was stated earlier in chapter 3
of this study. As the sole researcher, I was mindful of my special responsibility and made
conscious and consistently effort to ensure trustworthiness through all the progressive
stages of collection of data, transcription and analysis. My experience with the various
components of trustworthiness is summarized below:
Credibility
Earlier in this dissertation in chapter 3, I had cited Patton’s (2002) comment that the
credibility of qualitative research substantially depends on the researcher, who is the
primary instrument of research. I remained conscious of this critical need throughout the
opening, developing and closing stages of the study. I was able to successfully address
possible threats to internal validity in the case of this study. The first anticipated concern
for internal validity was the possibility of my own enthusiasm/over-enthusiasm about the
dire need and urgency of containing the emerging diabetes pandemic in India. This was
ensured by maintaining a stoic and completely professional stance during the stages of
selection of participants, interviewing and data collection process and finally through the
stages of analysis and interpretation.

106
The second anticipated concern was that the proposed research questions might
not evoke adequate interest among participants. This apprehension turned out to be
unfounded and the response to the research questions and the interview process was
complete with high level of participation by the interviewed participants. The third
anticipated concern was that as sole researcher and analyzer of data, my personal biases
and prejudices should not transfer to the study in any way including by way of non-verbal
cues and/or signals of body language. This did not happen and the data collection and
analysis were performed objectively and professionally.
Observing the participants diligently and conducting the interviews professionally
as per the protocol approved by Walden IRB ensured reliability of the study.
Observations, interviews, and planned visits to appropriate settings helped me gather
detailed and descriptive data. The transcribed data were reviewed with the participants
for clarification and to confirm accuracy of transcription. This further strengthened the
credibility of the research, transcription and analysis. The only external threat envisioned
was disdain for other systems of medicine by practitioners of a particular system. This
was not experienced during the course of this study.
Transferability
As stated in chapter 3, the transferability of the study and its findings to related
contexts and research situations were essential to the process of research. Transferability
reflects the strength of design of the study, its assumptions, and the process followed for
selection of participants and collection of data. By providing explicit details and specifics
of the assumptions, sampling strategy, and the thought process followed to determine the

107
research design of the study, I ensured the transferability and reproducibility of the study.
In the study, I have clearly identified the constraints and limitations encountered during
the process of collection and analysis of data. These details will make it easier for any
researcher or reviewer to seek transferability of this study. As seen and reported in
chapter 1, the global phenomenon of diabetes and the scale and enormity of its challenge
calls out for wide and expansive collaborations and corroboration between and among
researchers and other stakeholders. The required information in preceding chapter and
description of its execution in the current and later chapters will ensure transferability of
the study to any other locale where the study or any of its components needs to be
recreated.
Dependability
I noted in chapter 1 that the monumental challenge posed by diabetes in India and
the world is engaging global attention from many stakeholders, the policy planners,
global and national institutions, academic researchers and the solution providers. Diligent
conformance to the protocol that was laid out and detailed in the earlier parts of the study,
and accurate transcription and analysis of the collected data helped me ensure the
dependability of this study. The conscious effort made to prevent my preconceived views,
notions or prejudices from impacting the process of study and/or its eventual findings
helped the process. I kept detailed notes of interviews along with audio recordings of the
interview, where allowed, and the observation sheets. Dependability of the study was
significantly aided by maintaining clear focus on the research questions and observance
of research process as laid out in the design.

108
Confirmability
!The interviews were audio-recorded wherever possible so that all transcripts
accurately captured the responses from the participants. Where audio recording was not
permitted, the accuracy of notes and answer was verified at the end of the interview
process. The time tested qualitative research tool of triangulation was also used to
validate confirmability. The triangulation was achieved through data collected during the
observation process and cross-referencing with the transcripts of interviews and
comments from the peer group during the process of coding and analysis. The data
generated during the literature review process were also factored in the triangulation
process. The collected data from diverse individuals and settings supported the
confirmability!factor!of!the!study.!The!extension!of!participant!pool!from!35!to!36!
helped!achieve!saturation!and!completeness!of!data!as!also!helped!established!the!
confirmability!factor.!
Results
Results mark the finale of data collection and analysis process. “Qualitative
research involves the collection, analysis, and interpretation of data that are not easily
reduced to numbers.” (Anderson, 2010) The two research questions of this study were as
follows:
• How can the modern and traditional medicine approaches be combined to
contain the proliferation and immensity of the emerging diabetes pandemic in
India?

109
• What are the challenges and barriers of combining the methodologies
articulated in the traditional systems AYUSH and the modern system of
medicine in containing diabetes?
The above research questions were studied using the five-question questionnaire
and the responses to the questions have been summarized. The following are the detailed
results and findings of the 36 interviews in context of the two research questions.
Findings Related to Research Question 1
The analyses of data brought out the many ways in which the modern and
traditional medicine approaches could be combined to contain the proliferation and
immensity of the emerging diabetes pandemic in India. All participants commented on
the methods and process that could be used to combine the modern and traditional
approaches of medicine to manage diabetes. The participants stated that the emerging
pandemic of diabetes was an urgent public health concern in India. The participants
commented that effective efforts for managing and reversing the growth rate of diabetes
and efforts beyond current framework are needed to contain the growth rate of diabetes in
India. Analyses of data revealed that all medical traditions have guidelines that can be
used jointly to prevent and manage diabetes in Indian adults in age groups of 25-45 years.
The data showed the view of participants that integrative approach was a good
solution but needed careful and well-regulated execution and implementation. One of the
participants suggested that all physicians be asked to take short courses in other systems
of medicine to build appreciation for integrative medicine. Another participant favored
conducting of joint continuing medical education seminars. Many participants suggested
110
setting up of pilot integrative health centers where all systems are practiced and made
available to patients to build awareness of integrative methods. Analyses of data brought
out the importance of education and awareness of integrative approach to be created
among the patients and the community. Some of the participants’ felt that creation of
diagnostic labs be made available in remote areas will facilitate wider utility of
integrative approach.
The analyses of interview data and observation notes brought out that the favored
methods of combining medical traditions for an integrative approach to tackling diabetes
would be to approach this by way of patient interaction guidelines from the central
councils of medicine and by placing information materials in doctor’s clinics and
hospitals and by creating a mass media campaign.
Figure 18. Recommended steps for combining modern and traditional methods.
G !on!
!care!and!
!
• Through!central!councils!of!medicine!
• Supported!by!state!and!national!regulators!
P !Handouts!
!Prevention!
!Treatment!
• For!placement!in!clinics,!nursing!homes!and!hospitals!
• Providing!guidelines!from!different!medical!traditions!
P !Awareness!
C !against!
!
• Mass!educational!campaign!
• Social!media!awareness!campaign!

111
Findings Related to Research Question 2
The second research question sought data on the challenges and barriers of
combining the methodologies articulated in the traditional systems AYUSH and the
modern system of medicine in containing diabetes. Analysis of data showed that 34 out
of the 36 participants agreed that there were few significant but surmountable challenges
in deploying an integrative approach. Two participants did not see any significant
challenges or barriers. Analysis of data brought out that 35 out of the 36 participants
agreed that policy framework changes would be required to implement an integrative
approach.
The challenges and barriers of combining the methodologies articulated in the
traditional systems AYUSH and the modern system of medicine in containing diabetes
were; lack of trained personnel and resource persons, anticipated lukewarm interest
among medical professionals to know about other traditions. General lack of awareness
and knowledge of integrative approach, both among patients and physicians, was
identified by participants as a barrier. The barriers are depicted below in a figure.
112
Figure 19. Challenges in implementing integrative approach.
Summary of Responses to Questionnaire
The responses to five questions by the participants from all segments are
summarized below in tabular form. The responses are summarized by question for each
category of participants. Table 2 captures key comments that emerged from analysis of
data.
Question 1. What are the main guidelines in your medical tradition that might
help prevent occurrence of diabetes among Indians in the age group of 25-45 years?
C !
!among!
!traditions!
• Some!of!the!conceptual!principles!of!medical!
traditions!are!different!
• Areas!of!compatability/nonVcompatibility!
I !of!diet!
!lifestyle!
• Criticality!of!diet!and!lifestyle!in!treatment!in!AYUSH!
• Desirability!of!diet!and!lifestyle!in!other!systems!
A !of!
!
• Possibility!of!crossover!from!diabetes!to!other!
disease!areas!!
• Misuse!by!subVoptimal!medical!talent!

113
Table 2
Summary of Responses to Question 1
Medical tradition
Responses
Modern medicine
Diet, fitness, regular testing, monitoring, review of family history
Ayurveda
Prakriti determination, moderation in diet, balanced lifestyle, avoidance of
stress, prophylactic supplements like Triphala
Yoga
Specific exercises for pancreatic health, overall fitness, regularity of fitness
regime, moderated eating, daily routine
Naturopathy
Maintain gut health, practice detox diet once a year, more raw foods, stay with
five elements
Unani
"Diabetes in Unani is called zayabetus; diabetes is caused by stress, anxiety,
strain and tension, Soo-e-Mizaj-e-Kuliya, overeating, excessive use of alcohol,
sedentary mode of lifestyle"
Siddha
In Siddha, diabetes is referred to as Madhumegam.
Insulin metabolism is the principle for prevention and treatment of diabetes
management of a disease depends on the medicine and includes modification of
food, habits, and lifestyle as well.
Homeopathy
Homeopathy regards diabetes as treatable in many conditions and therefore
seeks intervention at early stages. Apart from prudent management of diet and
lifestyle, particularly in high-risk families where there is history of diabetes,
homeopathy does not offer any specific suggestions or guidelines on prevention.
Policy/administrators
Presently the National Health policy has no guidelines for patients becoming or
suffering from diabetes. Those patients who can’t afford to pay private
practitioners can seek treatment from state owned hospitals - both modern
medicine and traditional medicine at highly subsidized or no cost. As the disease
has not yet been officially declared as a pandemic or an epidemic, there are no
reporting and registry guidelines.

114
Question 2. Please list five important preventive actions, as stated in your system
of medicine, by practicing which a person can minimize the risk of becoming diabetic.
Table 3
Summary of Responses to Question 2
Medical tradition
Responses
Modern medicine
Prudent eating, regular exercise, regular clinical review, periodic testing,
awareness campaign.
Ayurveda
Moderation in food, eat in accordance with Prakriti, regular exercise, eat raw
food, lead a balanced life.
Yoga
Daily practice of physical yoga, practice of yogic breathing, meditation and
relaxation techniques, raw food, light dinner.
Naturopathy
Stress-free life, harmony within, embrace five elements in daily living, live
close to nature, eat naturally.
Unani
Syzygium cumin, Momordica Charantia, Azadirachta indica, Gossypium
herbaceous, Aegle marmelos are the plant sources that can prevent diabetes.
Siddha
In Siddha tradition, the five main preventative herbs are Jambolinor Naval
(Syzygium cuminii). Sarkarai Kolli (Gymnema Sylvestre), Kadalazhinjil or
Eganayakam (Salacia reticulate), Seenthil or Amrithu (Tinospora cordifolia),
and Vilwam (Aigil marmalose). In Siddha, siesta is not considered good for
diabetes and is generally discouraged.
Homeopathy
Homeopathic medicines help in maintaining the levels of sugar, protein and fat
metabolism and also help in preventing further progress and hence
complications of the disease. It effectively reduces the risks associated with the
disease to the bare minimum. Strict restrictions in diet and regular exercising,
especially jogging or walking, are a must in diabetes management. In diabetes,
people suffer from obesity, blood pressure. Specifically, supplementation of
Magnesium, Vitamin B6, Manganese, Vitamin C & E, Zinc and Omega 3
through homeopathic medicines is helpful in preventing diabetes.
Policy/administrators
From a policy perspective, both the federal and state governments allocate funds
from the public health budget for multimedia campaigns to educate masses
about the steps required to prevent and/or treat diabetes. In the past two years,
AYUSH Department has carried out a 'try AYUSH' campaign to help patients
explore AYUSH as a possibility.

115
Question 3. What are your views on the coexistence and concurrent usage of your
medical tradition with other medical traditions in India that may help to address the
emerging epidemic-scale challenge of diabetes in India?
Table 4
Summary of Responses to Question 3
Medical tradition
Responses
Modern medicine
Good idea, feasible, will improve outcomes, pharmacological commonalities.
Ayurveda
Diagnostics tools, clinical trials, pathway studies.
Yoga
Yoga can coexist with all systems, catalyzes efficacy of other systems,
facilitates all other therapies, make patients more positive and receptive.
Naturopathy
Coexistence only partially possible, as there is no role for chemicals in health.
Modern tools of diagnosis are the meeting point.
Unani
Unani system is plant, herb, and mineral based and can coexist with all other
systems.
Siddha
Siddha and other traditional systems of medicine are recognized for their
effectiveness in treating chronic health conditions like diabetes. If diabetes is
officially declared as a pandemic and every patient visit to any physician -
modern or traditional has mandatory questioning/diagnosis or screening for
diabetes, it would help contain the growth rate of disease.
Homeopathy
By its very nature and philosophy, homeopathy is compatible with all systems
of medicine and is in practice used in combination with other therapies and
traditions. Homeopathic medicines are thought to strengthen the immune system
and to stimulate the body's vital force to heal itself based on the principle
"similia similibus curenter," which means “same cures same.” This paradigm is
used in modern medicine in production of vaccines. Homeopathy can be the
main, complementary or adjunct therapy for most chronic and acute health
conditions.
Policy/administrators
While this is an excellent idea that must be tried, the efforts in this direction so
far have been very limited and restricted to a few states like Rajasthan and
Maharashtra where modern medicine and Ayush physicians practice together in
primary health clinics and hospitals. The success of these experiments has not
yet been evaluated and it would be timely and appropriate to make an
assessment before rolling out a national initiative.

116
Question 4.What, in your assessment, will be the main challenges of combining
the modern and traditional schools of medicine to tackle the rapidly growing incidence of
diabetes in India?
Table 4
Summary of Responses to Question 4
Medical tradition
Responses
Modern medicine
Common acceptable protocol, misuse by untrained people, need robust oversight
mechanism, might wean people away from modern evidence-based medicine.
Ayurveda
Not enough exchange of information between and among traditions, common
forums unavailable.
Yoga
Acceptance of yoga by other traditions as a complementary therapy, adequate talent
pool of proficient yoga therapists, wider recognition of yoga as a medical therapy.
Naturopathy
Create greater awareness of naturopathy through educational curriculum. Give
wider media exposure to benefits of using naturopathy.
Unani
While patient population accepts both traditional and modern systems of medicine,
the practitioners of modern medicine do not see alternative traditions as
respectfully. If this can be achieved, Unani can work in tandem with all other
traditions—modern and traditional—as a part of a national containment strategy for
diabetes.
Siddha
The main challenges will be that health is a state subject in India and an advisory
guideline issued by Central Government faces an uphill task for execution and
implementation. A way needs to be found that central guidelines are uniformly
implemented throughout the country.
Homeopathy
There will be two principal challenges. First, that homeopathy is practiced by lot of
self taught people who have not received any formal education or training in
homeopathy. That is also the reason that this tradition is viewed as 'uncontrollable'
from a policy standpoint.
Policy/administrators
The main challenge is to prevent abuse of the system by some physicians who may
start prescribing medicines from systems they are not fully versed with. Some
states in India have recently created a framework whereby AYUSH physicians
undergo an accelerated module of pharmacology training in modern medicine. This
however works differently as it enables AYUSH physicians to prescribe medicines
from modern medicine. This process does not achieve the intended benefits of
combining the outreach of modern and traditional medicines. The challenge of real
integrative approach remains unmet.

117
Question 5. What are the policy changes that would be required to check the
incidence of diabetes in India?
Table 6
Summary of Responses to Question 5

118
Medical
tradition
Responses
Modern
medicine
Mandatory screening, mass media awareness campaign; guidance to physicians to talk about
diabetes with every patient, patient education handouts at all clinics.
Ayurveda
The policy initiatives that will need to be changed are: recognition of Ayurveda and Ayush as
complete systems of medicine; enforcement of stricter standards on Ayurvedic medicines; making
detection of diabetes as an integral protocol of investigation for all patients in the age group of 18 to
45 years; insurance reimbursements for Ayush treatments and medicines.
Yoga
Make yoga mandatory in all schools and colleges. All TV channels to carry yoga for health content
for one-hour everyday. Funding for yogic research for diabetes. Clinical Trials, School of Integrative
health at national level.
Naturopathy
Factor salient features of naturopathy in national integrative health agenda for diabetes. Encourage
cooperation and not competition among medical traditions.
Unani
Diabetes should be accepted and proclaimed as a national challenge in which all traditions are
welcomed to participate and play a role. The regulatory framework should be aligned appropriately
to facilitate this interaction. The patient education materials and campaigns should provide equal
weightage to traditional methods and systems.
Siddha
The key policy changes required are that Medical Council of India (for modern medicine) and
Central Council for Indian Medicine be asked to synchronize their strategies and guidelines to allow
full benefits of leveraging the scope and potential of complementarity.
Homeopathy
Two changes will be required. The Central Council for Research in Homeopathy should bring out
Standard Operating Procedures and Guidelines on how all registered practitioners should identify
and diagnose diabetes, irrespective of the reason of patient's visit. Second, the national formulary to
be used for treatment of prediabetics and diabetics should include well-established and proven
homeopathic medicines. With these two changes it should be possible to tame the runaway growth

119
in incidence of diabetes.
Policy/
administrators
The policy frameworks would need to be amended and modified at multiple levels. First, would be
clear guidelines on detection and diagnosis of diabetes by patients who visit modern and traditional
medicine practitioners. The second layer would be guidelines on treatment within the larger scope of
integrative medicine that uses both the modern and traditional approaches of medicine. The third
policy change that may be helpful is to make diabetes notifiable so that the data and patient's health
can be tracked in order to provide necessary help and support. The fourth policy change would be to
increase availability of medicines for prevention and treatment of diabetes both from modern and
traditional schools. The fifth and most important policy initiative would be to increase awareness
and information about diabetes through educational curriculum and mass media campaign both print
and electronic. The sixth initiative would be to harness the outreach power and capacity of 1 billion
mobile telephones to help contain the growing incidence of diabetes.
Summary and Conclusions
The study has generated very useful data in support of implementing an
integrative approach to addressing the emerging diabetes pandemic challenge in India.
The analysis of data from interviews brought out the pros and cons of using an integrative
approach with overwhelming support in favor of using the integrative approach. The data
supported the concept. The challenges in implementing an integrative approach, as stated
before are real but manageable with enabling regulatory support. The next chapter will
deal with a discussion on findings and also explain the conclusions and
recommendations. A comment in an editorial in the journal of ayurveda and integrative
medicine had the following to state: “Today India is poised for a transformational
revolution. Among many other priorities the new government is expected to focus on
rediscovery of the contemporary relevance of our cultural identity, indigenous
capabilities and aspirations of our people. Thus during 2014-2019 South Asian health
sciences like Ayurveda, Yoga, Unani, Siddha, and Sowarigpa are likely to receive a big
boost.” (Patwardhan, 2014)
.

120
Chapter 5: Discussion, Conclusions, and Recommendations
Overview
The purpose of this study was to assess the practicability of using an integrative
approach as a potential solution for India’s emerging diabetes pandemic. The case studied
in this dissertation was the emerging diabetes pandemic in India. Participatory action
research was used to engage with key stakeholders to evaluate both the practicability and
challenges of using an integrative approach combining the methods and outreach of
modern medicine with methods and outreach of traditional medicine (AYUSH) as a
potential solution for India’s emerging diabetes pandemic.
The study has filled a void in the scholarly literature as well as the policy
framework of healthcare in India by evaluating an integrative health delivery model that
seeks to combine modern and traditional schools of medicine to contain the growth of
diabetes in India. I addressed the background of the problem; the scale, enormity, and
magnitude of diabetes; and the AYUSH schools of traditional medicine in the first
chapter. In chapter 1, I also described the purpose and framework of the study and the
rationale for the choice of research method and the theoretical framework. In chapter 2, I
offered a comprehensive review of published scholarly literature on the subject of
diabetes to understand the areas of emphasis and the resonating themes used in research. I
reviewed 108 scholarly articles and identified a gap in scholarly literature that led me to
evaluate an integrative approach that seeks to combine modern and traditional medicine
as a method of dealing with the enormity of the diabetes challenge in India.
The findings of the study could potentially add significant value to the body of

121
knowledge for the containment of diabetes in India. In the third chapter, I detailed the
research methodology and framework together with the sampling plan and the steps for
data collection and analysis. The results of data analysis and the findings of the research
were reported in the fourth chapter. I conducted qualitative research by way of 36
detailed interviews covering all key stakeholders as participants of the participatory
action research design. Of the 36 participants, 30 were medical practitioners: five from
modern medicine and five each from the five constituent medical traditions of AYUSH.
The remaining six participants were policy planners and/or healthcare administrators, five
from the state sector and one from the private sector. I transcribed and analyzed data
collected during interviews. The data were carefully coded to inductively derive themes.
The analyzed data supported a compelling case for designing and implementing an
integrative approach involving modern and traditional systems of medicine (AYUSH) in
meeting the challenge of the emerging diabetes pandemic in India.
An integrative approach to addressing the diabetes pandemic in India was
welcomed and appreciated by the interviewed participants as a possible solution to
India’s emerging diabetes pandemic. The questionnaire designed to elicit answers to the
research questions also sought perspectives from participants as to what might be the
challenges, hurdles, and pitfalls in implementing the integrative approach. Analysis of
data identified challenges that would need careful attention before, during, and after
implementation of an integrative model. One of the anticipated sub objectives of
participatory action research was to put together a list of key actions available in various
medical traditions that could help prevent the onset of diabetes among high-risk and at-

122
risk populations. The objective of compiling a list of preventative tools for averting
diabetes was successfully met in this study; the compiled list has been attached as
Appendix O.
Discussion
As a researcher, I view discussing and understanding findings as a very important
aspect of research, both for scholastic and practical reasons. “Qualitative research is
useful to policymakers because it often describes the settings in which policies will be
implemented” (Murphy, 1998, p. 37). The key findings of this research and their practical
implications have been summarized at a later point in this chapter. The framework of
participatory action research (PAR), described in chapters 2 and 3, was the method of
choice for this study. This method, as stated in chapter 3, is used where there is active and
interactive involvement of community and stakeholders in a research subject oriented for
achieving or propelling social change. Participatory action research, as noted earlier in
Chapters 2 and 3, also helps in stimulating social change through stakeholder
engagement, and this study was a successful effort in that direction. The inclusion of
policy planners/administrators among the panel of selected participants ensured that those
responsible for policy decisions were fully engaged in this discussion. I propose to
provide an executive summary of research from the contents of this chapter to all
participants in the true spirit of the process of participatory action research. Walden IRB
approved of this mode of dissemination of the research findings.
Research Findings in Context of Reviewed Scholarly Literature
In the second chapter, I identified six broad themes after the review of scholarly

123
literature. The six themes culled from the reviewed 108 scholarly research papers were as
follows:
• Diabetes is a complex, multifactorial disease, and much remains to be done in
medical and scientific terms to explain its causation and find a permanent cure
for the various types of diabetes.
• Incidence of diabetes is much larger than estimated because of extensive
nondiagnosis in all parts of the world and noninclusion of high-risk
prediabetics in the count.
• Diabetes is a life-changing phenomenon for the patient, the family, and the
nation’s healthcare system, and therefore the educational and support needs of
the patient and community need to be well provided.
• Innovative solutions need to be explored to tackle the emerging pandemic of
diabetes in India.
• There are potential benefits of using complementary systems of medicine to
address diabetes.
• Literature supports the continued quest for breakthrough and innovative
methods to tackle the challenge of an emerging diabetes pandemic in India
and the world.
The peer-reviewed literature clearly brought out the enormity of the challenge
posed by diabetes in India and the rest of the world. Literature supported the need for
breakthrough and innovative approaches to significantly increase the impact of methods
that could halt and/or reverse the growth rate of diabetes in India and the world. Multiple

124
researchers evaluated the impact of different medical schools and traditions on the
management of diabetes. The gap identified after the review of literature was that there
was no published research to evaluate the possibility of an integrative approach
combining the methods and outreach of modern medicine with traditional medicine
(AYUSH) as a method to address the emerging diabetes pandemic.
This study was designed in keeping with this gap identified in the scholarly
literature. The choice of methodology and theoretical framework was also made in
keeping with the need to have a complete evaluation of the two chosen research
questions. The two research questions that this study strived to find answers for were the
following:
• How can the modern and traditional medicine approaches be combined to
contain the proliferation and immensity of the emerging diabetes pandemic in
India?
• What are the challenges and barriers of combining the methodologies
articulated in the traditional systems (AYUSH) and the modern system of
medicine in containing diabetes?
I used these two questions with the intent to determine whether and how the
modern and traditional medicine approaches could be combined in an integrative
healthcare model and what the challenges and barriers to this effort might be. The
selection of participants, questionnaire, interviews, transcription, and data analysis were
done to ensure the ability to answer the two research questions. The analysis of data
brought out that the modern and traditional approaches could be combined to contain the
125
challenge of an emerging diabetes pandemic in India. The themes of the reviewed
literature and the identified gap in scholarly literature were well addressed by this study,
as demonstrated in Figures 19 and 20.
Figure 19. Themes of literature review.
Diabetes'2'a'multifactorial'
problem'2'an'un4inished'
agenda'
Huge'incidence'of'disease'
with'large'undiagnosed'
numbers'
Life'changing'
phenomenon'for'patient'
and'family,'needing'
support'and'education'
Innovative'solutions'
needed'
Potential'bene4its'of'
using'complementary'
approach'
Need'for'continued'quest'
for'solution'
126
Figure 20. Findings of this study.
Interpretation of Findings
The analysis of data revealed a broad roadmap for implementing the integrative
approach that seeks to combine methods and outreach of modern and traditional systems
of medicine. The three stages of the roadmap that emerged from analysis of data are as
below.
First, the healthcare policy regulators and medical research councils of modern
and traditional medicine in India could be requested to issue guidelines to medical
practitioners, both for the modern medicine and traditional AYUSH practitioners. The
guideline could encourage all doctors to briefly discuss diabetes with every visiting
patient, the objective of patient visit to the clinician notwithstanding. In doing so, the
patient population will get highly sensitized to the risk of diabetes. Patients with primary
Findings!
of!this!
study!
Every'medical'
tradition'has'
preventative'tools'
and'for'avoidance'
and'management'of'
diabetes.'These'can'
be'widely'
publicized.'
There'are'policy'
concerns'and'
challenges'for'
implementing'
integrative'
approach'that'
would'need'to'be'
addressed.'
Integrative'
approach'has'the'
potential'to'open'up'
avenues'and'
possibilities'for'
further'research.'es'
Public'education'
and'greater'
awareness'of'
integrative'
approach'can'help'
improve'
preparedness'to'
meet'the'challenge.'
Integrative'
approach'is'a'
desirable'solution'
for'managing'the'
challenge'of'
diabetes.'

127
or clinical symptoms of diabetes or family history of diabetes could be encouraged to
undergo confirmatory tests for to determine the status of diabetes. Those with prediabetes
symptoms could receive dietary and lifestyle guidance as per integrative tools to help
them stave off the risk and challenge of becoming diabetic. The patients with confirmed
diabetes could receive guidance and medication for management of diabetes to minimize
or eliminate the risk of life threatening co-morbidities linked with diabetes. This could
result in lowering the risk of co-morbidities and lead to likely increase in the lifespan, and
quality of life of people with diabetes.
The second step could be to provide patients and at-risk population with handouts,
books, e-books, catalogs, and multi-media content on methods and tips for avoiding
diabetes as stated in both the modern and traditional schools of medicine. These handouts
could be placed at doctor’s clinics, nursing homes and hospitals and other places
frequented by people. The multi-media content could be played on radio, television, and
cinema as also relayed by way of text messages on the 900 million mobile phones in
India. The use of preventative methods will help in containing the incidence of diabetes.
The third step could be to increase awareness of diabetes through an information
and education campaign that could be coordinated by the public health machinery of the
federal and state governments in India. The campaign could draw content from best
practices of the modern and traditional systems of medicine. This could be by way of
educational content on diabetes in different medical traditions to be included in the
school curriculum and through social media campaigns of the public health agencies.

128
Challenges and barriers to implementing the integrative approach. A number of
challenges and barriers were identified during analysis of data that could potentially
interfere with smooth implementation of an integrative model that seeks to combine
methods and outreach of modern medicine with methods and outreach of traditional
medicine AYUSH to tackle the challenge of diabetes. The first challenge was that there
are a few noteworthy conceptual differences between and among various systems of
medicine. The modern medicine uses chemically synthesized drugs whereas naturopathy
favors use only of natural products and herbs. This could potentially limit the extent of
integrative approach in practice. The second challenge, as stated by a participant was that
“in traditional systems of medicine the do’s and don’ts of diet are very important in
treatment of diabetes, whereas modern medicine offers only broadly contoured dietary
guidelines.” The corrective mechanism in modern medicine is “primarily through drug
intervention”, as was stated by a participant. The third challenge that was articulated was
that “not all practitioners in the AYUSH schools of medicine or even modern medicine
have the right credentials to practice and participate in an integrative model” and
therefore “appropriate safeguards against potential misuse would have to be established.”
This was the comment offered by another participant.
The barriers stated above are both real and serious, but as stated by a participant
“manageable.” The success of an integrative model stated a participant “would require
careful monitoring and oversight.” A policy administrator commented, “The true metrics
for success of integrative model would be in terms of marked reduction in the growth rate
of diabetes in India.”

129
Limitations
In the design of this study, I had listed three potentially limiting factors in the
context of validity of this study. First was the inherent limitation of qualitative research,
where the sample size is small when compared to quantitative or even mixed methods
research. However, for a research a situation like the one being studied here, it would not
be possible to use any method other than the qualitative method. This has been
adequately discussed in the Chapter 1 and Chapter 3 of this dissertation. The subject of
this dissertation required close interaction and discussion with medical practitioners and
policy stakeholders and the quality and intensity of data gathered during detailed
interviews could not have been obtained through the quantitative or mixed methods
approach. The limitation of small sample size was in essence an academic limitation. The
experience of research showed that sample size was adequate and data saturation point
was systematically achieved in this study. The snowballing approach gave the
opportunity to expand the sample size so that level of data saturation could be achieved.
The second limitation was that I was the single person responsible for collection
and analysis of data. This potential limitation was more to do with my personal research
integrity and ability to remain completely professional and objective during the course of
this study. It was very important for me to keep all my “researcher biases” at bay. This
objective was successfully achieved and both the interviews and data analyses processes
were completed without any bias or pre-conditioning from my personal perspectives or
views.
The third limitation was the omission of newest component of AYUSH – Sowa

130
Rigpa, the Tibetan school of medicine was not studied specifically in the data collection
and analysis process. As seen in the definitions section of Chapter 1, Sowa-Rigpa
appeared to be compatible with the other AYUSH constituent systems and could after
appropriate research be drafted in to the integrative model.
Social Change
One of the key objectives of this study was that the participatory action research
process, interviews and analysis of data should result in positive social change. In the
chapters 1 & 3, some expectations were stated for the potential of this study to contribute
to positive social change. I could clearly perceive the build-up for positive action on
social change as I went through the process of data collection. In my assessment, the
study has generated keen interest and in some measure sown the seeds for starting
positive social change. The study has created a body of information that will increase the
medical touch points for patients who need medical assistance or help. Medical
practitioners of different traditions, as a result of the interviews and findings were able to
communicate key preventative measures regarding diabetes in their respective traditions.
The preventative tools could be further refined and offered for larger good of the patient
population in India. The key preventative steps recommended by practitioners have been
summarized and restated in the Appendix 8 as one of the key outcomes of this study.
The study has successfully drawn the attention of policy administrators to the
need of aligning and fine-tuning the policy initiatives that would likely “result in wider
and beneficial implications for India that is battling the scrooge of diabetes”, as aptly
stated by a participant.

131
The study, as stated by a participant “might inspire researchers to suggest
integrative, wholesome and affordable approaches to preventing the incidence of diabetes
and possibly other forms of non-communicable diseases in the future.” The study has
generated high level of interest and its eventual publication will bring its
recommendations into the wider public domain and be of “great interest to the
community of researchers and scholars,” as commented by a participant.
The social change factors of this study will also arise, as envisaged before, and as
confirmed by a participant “ by way of increased acceptance of traditional medicine by
people, practitioners, policy makers and the society.” “The more inclusive medical
engagement of various traditions will lead to a new beginning in India” was the comment
offered by another participant. The comment made by a policy planner participant of the
study was, “gradually an integrative approach will begin to receive wider support both
from the state and the society.” This study has made available valuable information on
prevention and management of diabetes from both streams of physicians (modern and
traditional medicine) and public health policy administrators. The study has added to the
body of knowledge that may help, as stated by a participant “in prevention of a chronic
lifelong disease and result in positive social change both in the public health scenario and
in the lives of the individual and the community.” The collaborative efforts in the future
“could lead to joint clinical trials to validate the efficacy of traditional methods and
medicines,” was a comment by one of the participants. This could “inspire greater
confidence in usage of traditional medicines and ensure better quality of products and
services that would benefit the patient community in India and the world” was a

132
participant comment.
As demonstrated in the reviewed literature, research of this nature has the
potential of causing positive social change in the lives of people by highlighting and
publicizing well-researched modes of diet and lifestyle changes as championed by
various medical traditions (Hu, Wallace, & Tesh, 2010). Innovative ways of prevention
and containment of diabetes will save valuable socio-economic resources in the large
developing economy of India (Shetty, 2012). IDF (2011) is of the view that diabetes is
not only a health crisis; it is a global societal catastrophe. The ability of this study to
potentially result in positive social change is clear from the above analysis.
Future Action
The study has paved the way for compilation of guidelines on prevention and
treatment of diabetes as per different health traditions of India. The indicative guidelines
provided in the Appendix 8 can be expanded into a very useful document that could
become an important aspect of using integrative approach for containment of diabetes.
The guidelines could be illustrated with visual content to make them better and easier to
grasp by all shades of Indian population. The model of integrative approach could be
developed further with more specificity and operational details. A pilot implementation
of integrative approach could provide useful data and information for is national rollout.
One of the participants recalled a comment from journal of ayurveda and integrative
medicine (JAIM) in this context “A rational policy for promoting integrative medical
practice based on new models of medical education needs to be formulated and
promoted.” (Patwardhan, 2014)

133
Scope for Further Research
The study has also opened up further avenues for research. The further research
could take place in the area of integrative approach to diabetes or using integrative
approach for other health conditions and non-communicable disease or even integrative
approach as a method of designing and implementing public health policy. A participant
referred to a published comment in JAIM that “AYUSH professionals should be
encouraged to do robust documentation of clinical experiences, observations, case studies
and procedures, so that sufficient evidence for practice is established.” (Patwardhan,
2014) The study could lead to further research in all countries and geographies where
traditional medicine is available as a means to complement and augment the healthcare
delivery. The further research could be in the areas of joint clinical trials and
development of integrative drugs and vaccines.
Conclusion
There is a visible global shift from alternative medicine to integrative health. The
holistic wisdom of traditional schools like ayurveda, yoga and other AYUSH traditions
offers a rich source of experience, wisdom and capabilities that are crucial for initiating
enduring transformational change (Patwardhan, 2014). Innovative approaches where
Indian health systems and modern medicine synergize together can realize the dream of
futuristic integrative health systems. (Patwardhan, 2014)
Every modern society, community and nation is working to provide a better
model of healthcare for its people “Health and healthcare systems are essential pre-
requisites for a happy, successful and prosperous nation and world. Innovative and

134
creative thinking and solutions hold promise for a new tomorrow and a new
commencement”, was the comment from a participant of this study. This study has
reached the conclusion that there is a powerful case for trying integrative approach
combining methods and outreach of traditional and modern medicine. AYUSH research
deserves a prominent place in national science laboratories and modern medical schools.
(Patwardhan, 2014) This study may open many new vistas for developing future
strategies of healthcare in India and other countries. I learnt during the course of
interviews and data collection that while new inventions are important, harnessing time
tested age-old traditions is equally essential. This study has recommended combining
modern and traditional medicines for a nation that is deeply rooted in its tradition and
culture in all aspects of its cultural and social life. “Countries like China and Korea have
very boldly integrated traditional and modern medicines. India may also need to discover
its own model of integration.” (Patwardhan, 2014)
An integrative approach combining modern and traditional methods of medicine
will ensure better quality of life for the people with diabetes and will help in prevention
for people diagnosed with pre-diabetes. A participatory and collaborative approach
amongst physicians of different streams of medicine will support a patient-centric
healthcare system. AYUSH has universal value and potential to provide innovative,
holistic and affordable healthcare. This is possible not by any political declaration but
only if an open, scientific, critical, approach and a continuous quest for right evidence is
practiced. (Patwardhan, 2014) With adequate training of modern medicine and tools of
modern medicine made available to practitioners of traditional schools of medicine and

135
frequent interactions so as to benefit the patient will enrich the doctors and will enhance
the knowledge of the patient regarding their health conditions.
India is a large nation, rooted in ancient traditions and cultural richness. It has an
abundant availability of skilled resources in varied systems of medicine, and the most
modern medicine with all its tools and technology. Physicians, scientist, and policy
planners could come together to implement the integrative approach. The integrative
approach has the potential to successfully address the emerging diabetes pandemic in
India.

