


1
PERCEPTIONS OF ACCESS TO HEALTHCARE IN CAMEROON BY WOMEN OF
CHILDBEARING AGE
Chapter 1: Introduction to the Study
Introduction
For over 30 years, access to healthcare by Cameroon’s women of childbearing age (WCBAs) has
remained a significant health challenge. WCBAs in a majority of countries in the global south,
including some developed countries, are facing challenges related to healthcare access, even in the
presence of well-developed infrastructures, technologies, and economies (Imo, Isiugo-Abanihe, &
Chikezie, 2016). Reasons for these challenges include that the majority of medical innovations,
developments, and information are only discussed theoretically rather than being fully and practically
incorporated into the healthcare sector. Cameroon, located in central Africa, with an estimated
population of 21.7 million inhabitants, is facing the same challenges related to healthcare access (Koh
& Nowinsky, 2010).
Maternal and fertility health continues to be a major public health concern among WCBAs
(World Health Organization [WHO], 2012). The WHO indicated that, each year, about 8 million
women suffer from pregnancy-related complications, and over 500,000 maternal deaths occur, many
of which could have been prevented with adequate healthcare (Abrokwah, Moser, & Norton, 2016).
This situation is also occurring in the rural communities of Cameroon. This chapter contains relevant
background information, current health problems in Cameroon, social determinants of health in
Cameroon, problem and purpose of the study, research questions, and a conceptual framework to guide
the design and address the research questions. This chapter also defined key terms used in this study.
Background of the Study
Women’s health should be taken seriously by every nation’s political and health leadership.
Comprehensive care promotes good health for women and their families throughout their lives, from
prevention of premature delivery and low birth weight to childhood nutrition and immunization and

2
prevention and treatment of chronic conditions such as heart and lung disease, mental health disorders,
diabetes, and cancers
(Quick et al., 2014). Like many other countries, Cameroon’s WCBAs have struggled with poverty,
unemployment, lack of sufficient social services, and minimal investment in social amenities
(Tchombe et al., 2012; Ukpere, 2011).
Cameroon’s women who have reached the age of childbearing are some of the most adversely
affected demographic populations (Chandra-Mouli, Camacho, & Michaud, 2013). Poverty and lack of
healthcare has mainly affected women living in rural areas who have difficulty accessing public health
services due to a number of challenges: (a) distant health facilities, (b) lack of funds to settle medical
bills, (c) poor knowledge of public health, and (d) lack of means to reach hospitals (Egbe, 2014). For
these reasons, many women often depend on medical aid such as maternal and child healthcare
services from health service providers, primarily religious organizations and non-governmental
organizations (NGO) personnel who travel to villages (Soh, 2013).
The health of WCBAs in the southwest region of Cameroon is of great concern and limited
data exists regarding how women in these regions perceive their health and healthcare access (Deaton
& Tortora, 2015). WCBAs in Cameroon, particularly in poor rural communities, have limited access
to healthcare facilities and services that cater to their healthcare needs (Weinger & Akuri, 2007).
WCBA do not consider healthcare to be their fundamental human right (Soh, 2013).
To improve modern healthcare awareness and minimize gender inequality in healthcare provision,
Cameroon is interested in changing perceptions and access to healthcare among WCBAs (McTavish
& Moore, 2015; Soh, 2013). Efforts to improve healthcare access in the southwest region of Cameroon
have received support from independent organizations such as the Cameroon Healthcare Access
Program and the WHO (Abrokwah et al. 2016). To effectively evaluate the healthcare access problem,
it is important to also understand related challenges to improve the level of health services in the
country. These challenges have led to low levels of acknowledgment of modern health services and

3
reduced access to services among WCBAs. In light of these challenges, this study focuses on
understanding perceptions about access to healthcare among WCBAs in the southwest region of
Cameroon.
Current Health Problems in Cameroon
Stakeholders widely recognize that factors contributing to high maternal mortality include the
low quality of service during delivery and the lack of healthcare facility access for WCBAs in
Cameroon (Egbe, 2014). For example, from 1993 to 2003, childbirth with medical practitioners
increased from 85 to 90% for the richest quintile, but fell from 25 to 19% for the poorest (Ajong,
Njotang, Kenfack, Yakum, & Mbu, 2016). Also, 45% of pregnant women wait until the second or third
trimester to seek prenatal care, when it is often too late to adequately anticipate complications (Ajong
et al., 2016).
In general, access to medical services for many WCBAs in developing countries is low (Soh, 2013).
The
extreme shortage of primary care doctors, lack of infrastructure, corruption, low per capita health
expenditure, and economic growth aggravate problems with access to care (Business Monitor
International, 2014; Poverty and Health, 2013; World Justice Project, 2013). Cameroon has one of the
most notorious reputations in Africa in terms of poor maternal healthcare. The country has made global
headlines a number of times involving health indicators of countries in the global south, due to the
deaths of pregnant women who were unable to access healthcare services (Business Monitor
International, 2014; Poverty and Health, 2013; WHO, 2012; World Justice Project, 2013). The
country’s Ministry of Public Health indicated that 9,000 women died during childbirth in 2010 (Leina,
2011). Further, the government “attributes its maternal mortality problem to the absence of adequate
maternal care” (Leina, 2011, p. 1). Some reasons women prefer not to seek healthcare services include
the lack of societal permission to do so, poverty, distance to health facilities, and fear of going alone
(Ibrahim et al., 2013). Therefore, a need persists to understand WCBA perceptions regarding their

4
access to healthcare, which is clearly affected by the current healthcare system and related
mechanisms.
Nurses are the primary providers of healthcare services and in Cameroon, the nursing profession is
facing funding shortages because the government has dedicated only 6% of expenditures to healthcare
(Ajong et al., 2016). A majority of healthcare facilities in Cameroon are charging high prices, and as
a result, poor families are turning to traditional healers and self-healing methods (Ajong et al., 2016).
In addition, poor water quality and sanitation is causing women’s poor health (Kruk, Porignon,
Rockers, & Van Lerberghe, 2010). Only 40% of the population is receiving pipe borne water (Ajong
et al., 2016). The remaining population lives in areas using improper sanitation practices. All of these
issues contribute to a decreasing life expectancy of the population by 2 years (Kruk et al., 2010).
This study could help the Cameroon legislature consider the healthcare system and its effects
on WCBAs. As a result of this study, the healthcare success of Cameroon women may increase through
the creation of new laws. This study may also serve as a guide to healthcare advocates who are working
to improve the health status of Cameroon. These efforts can bring dramatic changes to the healthcare
system of Cameroon.
Problem Statement
WCBA in Cameroon, particularly those in poor rural communities, have limited access to healthcare
facilities and services that cater to their healthcare needs (World Bank, 2013). Although a vast majority
of these women have concerns about their health and recognize a variety of factors that endanger their
health, they have previously had little information regarding how to seek healthcare services. Instead,
they place the burden of maintaining their health on themselves (Weinger & Akuri, 2007). Therefore,
most WCBAs will not perceive government healthcare services as an option in maintaining their
health. Mismanaged healthcare facilities as well as women’s sociocultural status in terms of healthcare
access and financial vulnerability impact this population negatively (Soh, 2013).

5
Despite a growing need for a sustainable and affordable healthcare system that meets the basic
healthcare needs of WCBAs who need medical care, a gap persists in understanding the reasons
involving inaccessibility issues and how such issues have influenced the personal satisfaction and
health awareness frameworks that do exist. Literature from government reports in this area are limited,
and directing an investigation into healthcare access for WCBAs could reveal essential factors
regarding how this populace sees current medical services in Cameroon and their view of what
potential outcomes exist for making change.
Purpose of the Study
The purpose of this qualitative study was to examine how WCBAs seeking healthcare services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. Also, this study discerns how WCBAs perceive access to healthcare institutions.
Examining how WCBAs in Cameroon perceive the quality of the healthcare services offered and how
this impacts their quality of life is significant. A study of this nature may provide data useful in
recommending solutions to the problems involving shortages of healthcare professionals,
infrastructure, economic conditions, financial discrepancies, access to technology, and management
of the system.
Research Questions
I formulated three phenomenological study questions, which I used to obtain the responses
needed to understand the perception of access to healthcare by WCBA in rural communities in Mamfe
Cameroon.
RQ1: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the process
of
healthcare access through health institutions?
RQ2: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the quality
of
healthcare services offered through healthcare institutions?

6
RQ3: How do WCBAs seeking maternal/child healthcare services in Cameroon understand the
impact
of healthcare services on their quality of life?
Theoretical Framework
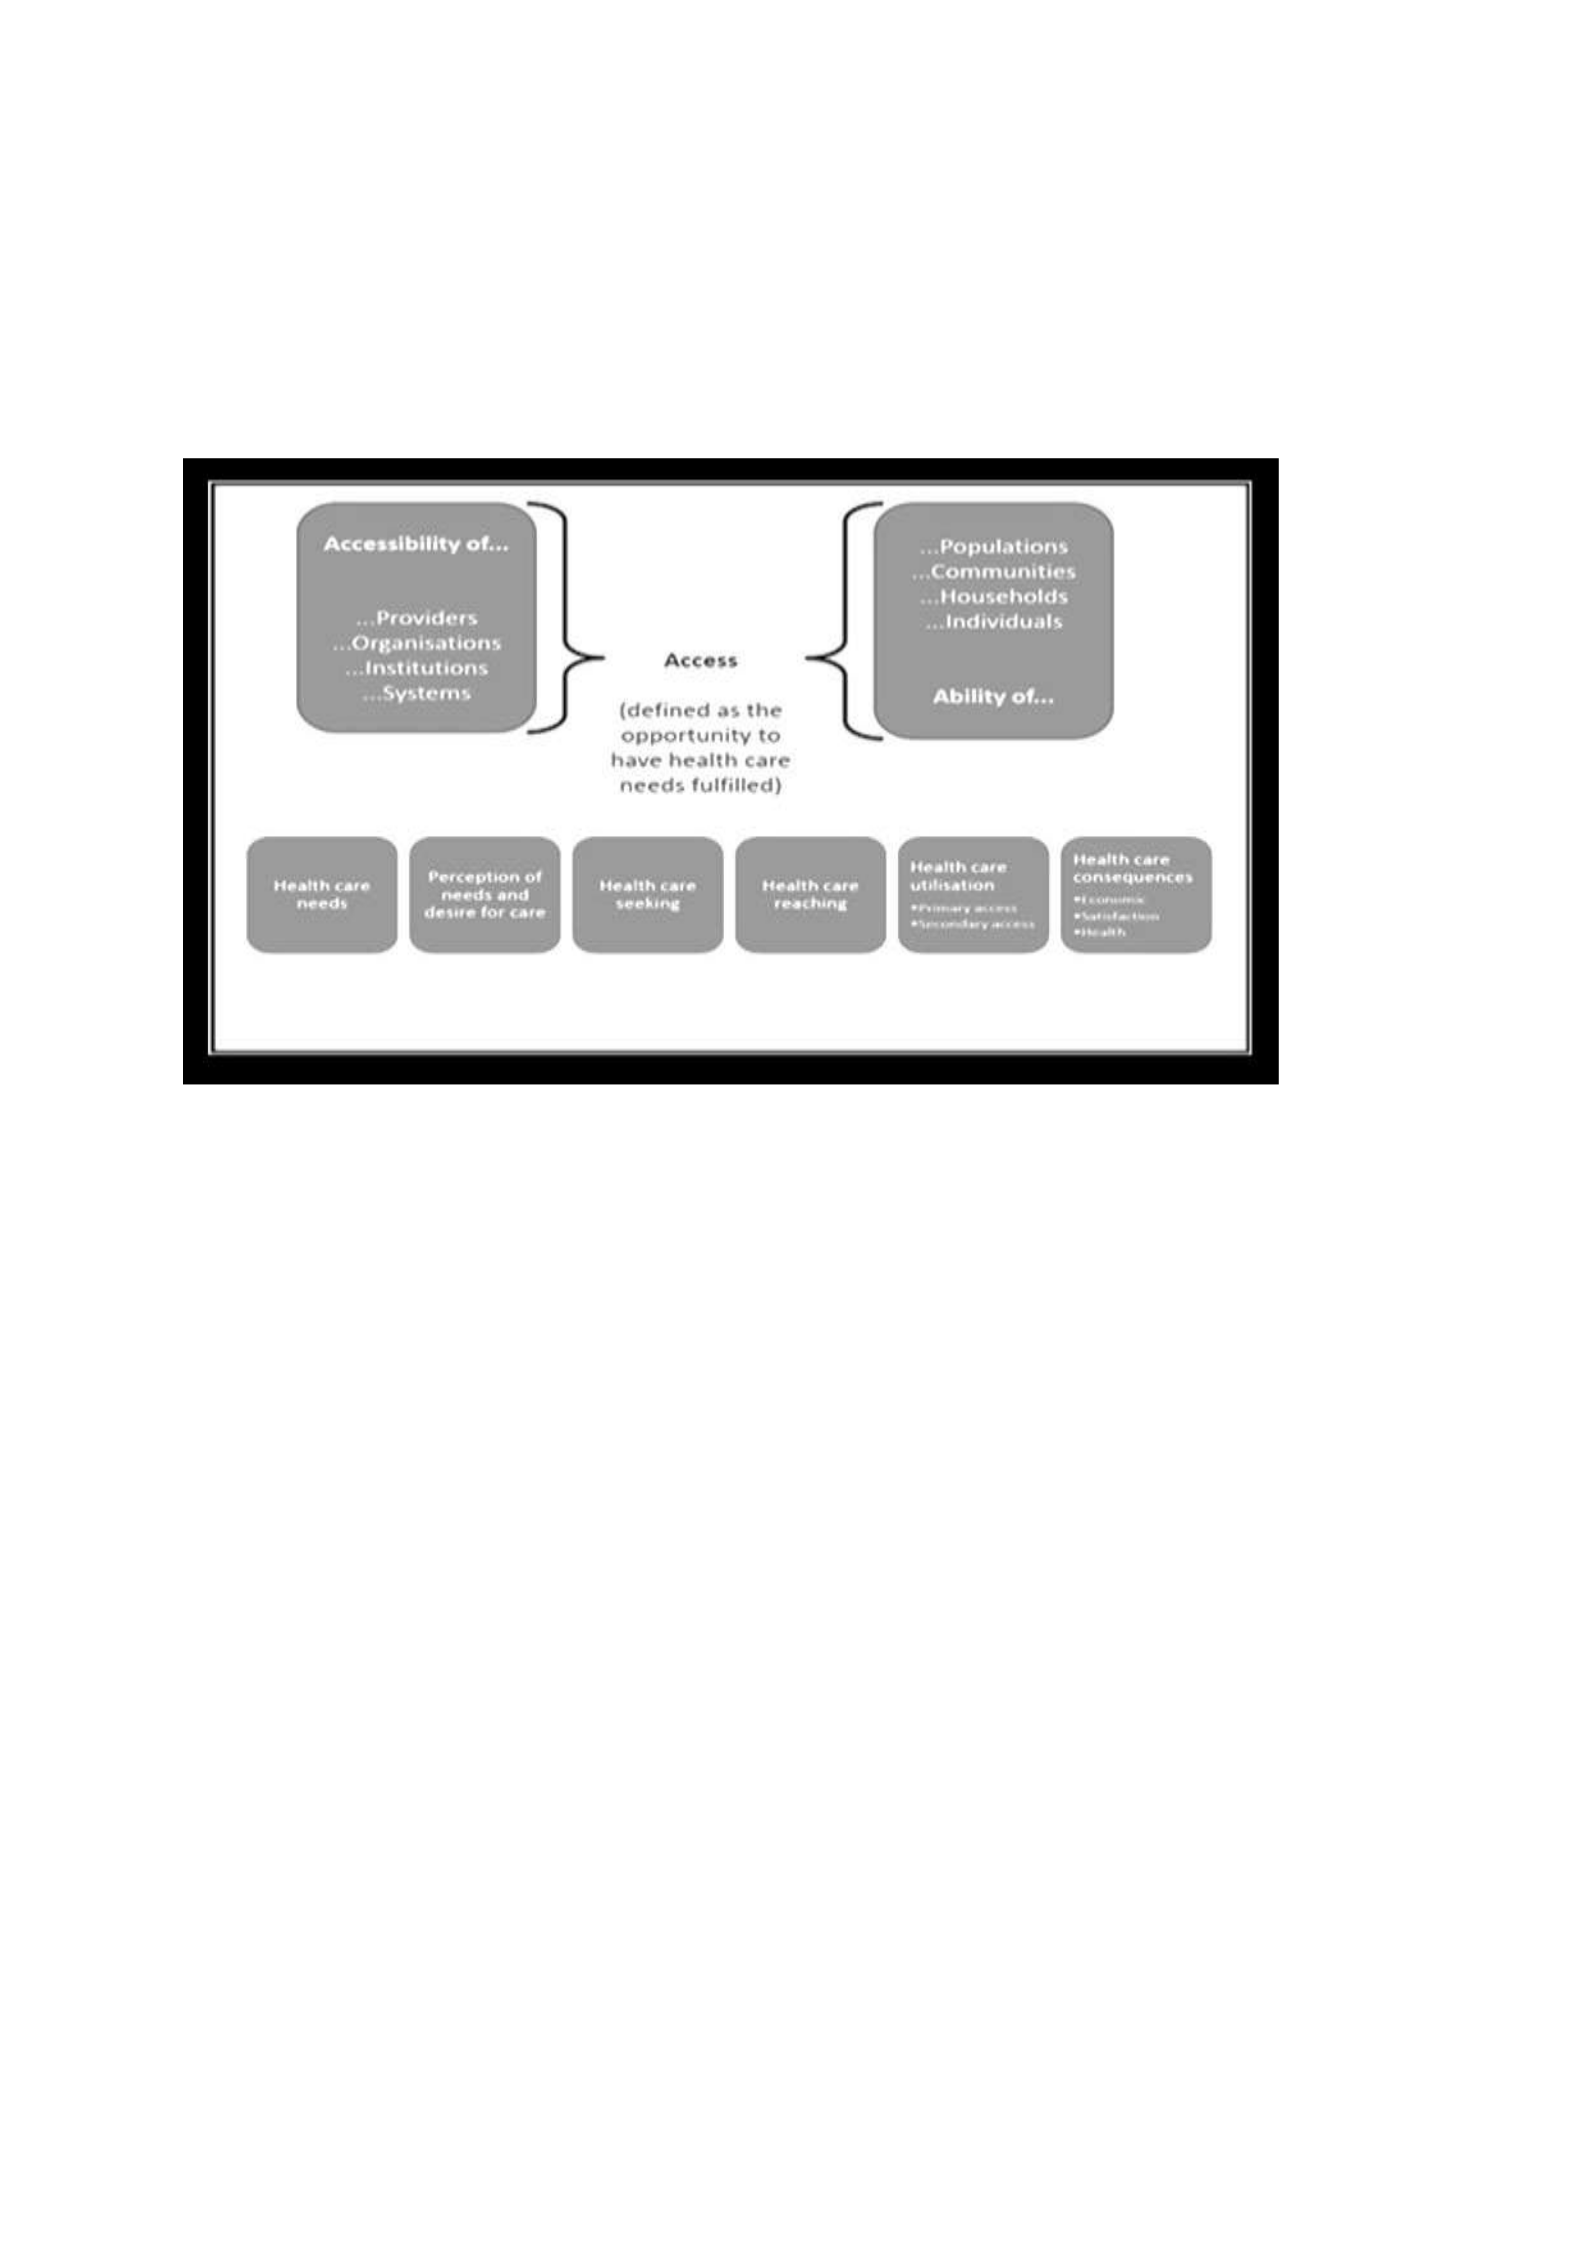
The conceptual framework for this qualitative study was Andersen’s healthcare utilization
model. Andersen & Newman (2005); Rigg, Cook, & Murphy (2014), viewed the idea of access in a
variety of ways. According to Andersen & Newman (2005), the characteristics of a population as the
major factor in designing the access framework. Rigg et al. (2014) believe that health outcomes should
be the main determinants of a healthcare access model Despite ongoing debates regarding the concept
of access, the healthcare sector accepted the notion that the reach of urban and rural healthcare
facilities, medical personnel, and quality of healthcare service differs markedly.
According to Aday and Anderson (1974), financial ability is a significant indicator of the level
of access to quality healthcare, which further defines the boundary of access to healthcare between
urban and rural populations. Use of the healthcare utilization model allowed me to address (a) how the
process of healthcare access is perceived by WCBAs in Cameroon, (b) how the quality of healthcare
is perceived by WCBAs in Cameroon (c) how WCBAs understand the impact of healthcare services
on their quality of life. This conceptual model recognizes access as involving the relationship between
characteristics of the healthcare service system and potential users in a specified area, moderated by
healthcare public policy and planning efforts (Pemunta & Fubah, 2015).
The knowledge obtained through qualitative methods illuminated the intersectionality of problems
such
as poverty and suffering, and people’s inability to access appropriate healthcare, thereby providing the
basis for planning and implementing equitable care at local and national levels. Contextualized
knowledge also helps one appreciate the strength and agency that individuals possess in relation to
their health and healthcare. An examination of the lived experiences of WCBAs using the healthcare
utilization model provided a more nuanced view of women’s access to healthcare in Cameroon

7
(Levesque et al. 2013). This perspective was useful because this multilayered analysis gives insight
into how class and gender identities, among others, determine the social and material conditions of
women’s lives and makes explicit how complex interdependencies organize WCBA experiences. This
model was helpful in attaining a comprehensive understanding of the reasons for poor access of
Cameroonian women to healthcare services. This framework was also helpful in analyzing the
perspectives of Cameroonian women about the quality and impact of healthcare services.
Andersen’s conceptual framework also focuses on the individual as the unit of analysis and
goes beyond healthcare use, adopting health outcomes as the endpoint of interest (Pemunta & Fubah,
2015). The framework added genetic susceptibility as a predisposing determinant and quality of life
as an outcome (Pemunta & Fubah,
2015). By using the framework’s relationships, one can determine the directionality of the effect
following a change in an individual’s characteristics or environment. For example, if one experiences
an increase in need as a result of an infection, the Andersen model predicts this will lead to increased
use of services. One potential change for a future iteration of this model is to add genetic information
under predisposing characteristics. As genetic information becomes more readily available, it seems
likely this could impact health services usage, as well as health outcomes of study population (Pemunta
& Fubah, 2015).
Through this model, one can comprehensively examine the reasoning behind decreased accessibility
to
healthcare services. This model allows participants to openly share their opinions about current
healthcare status in Cameroon.
The health and medical field conventionally used the health belief model and Andersen’s
theoretical models to explain services use. The Andersen model, which explains that predisposing,
enabling, and need factors determine services use, is used broadly as a theoretical model that analyzes
predictors of health services use. The healthcare utilization model will be suitable when exploratory
8
research is needed due to lack of previous studies regarding perceptions of women about healthcare
services in Cameroon.
Figure 1. A graphical illustration of the healthcare utilization model. Note. Adapted with permission
from “Employment of Andersen’s description of the healthcare utilization model” by Levesque et al.
(2013), International Journal for Equity in Health, 12(1), 18.
Nature of the Study
This study used a qualitative phenomenological approach. The phenomenological methodology
allows
patients to express their issues related to healthcare services and ideologies related to quality health
(Rudestam & Newton, 2015). This methodology also permits patients to express their ideas about how
they give meaning to life events and how they perceive those events (Rudestam & Newton, 2015).
I explored perceptions regarding healthcare access or crises for Cameroonian WCBAs. Contextual
knowledge from target populations and key institutional actors in this rural setting in Cameroon could
inform the management regarding healthcare access challenges, health policy, and practice. This study
could inform the Cameroonian government and healthcare system of issues involving equity and

9
vulnerable populations during the development of strategies to increase interventions and reach
national health goals.
I used semistructured face-to-face interviews. Participants were encouraged to narrate their
personal experiences freely. Participants were WCBAs in Cameroon ranging in age from 18 to 45
years who could understand and speak English. It was necessary that participants speak and understand
English to facilitate communication and collect accurate data. I used a purposive sampling technique
and employed Colaizzi’s seven-step descriptive phenomenological strategy to describe and analyze
collected data.
Operational Definitions
Health Disparity: The differences adversely affecting socially disadvantaged groups which may
reflect
social disadvantage, but causality need not be established (Braveman et al., 2011). This definition is
grounded in ethical and human rights principles and focuses on the subset of health differences
reflecting social injustice, distinguishing health disparities from other health differences. According to
the National Institutes of Health (2015), it is the differences in the incidence, prevalence, mortality,
and burden of diseases and other adverse health conditions that exist among specific population
groups.
Global south: Developing or low- and middle-income countries. The term global south is also used
because of its significance from the postcolonial feminist perspective.
Healthcare access: Ability of a population to reach healthcare providers without financial,
organizational, social, or cultural barriers, and use services to preserve or improve their health
(Gulliford et al., 2012).
Health equity: The principle underlying a commitment to reduce and ultimately eliminate disparities
in

10
health and its determinants. Pursuing health equity means striving for the highest possible standard of
health for all people and giving special attention to the needs of those at greater risk of poor health
based on social conditions (Braveman, 2014).
Maternal/child health: Maternal health is the health of women during pregnancy, childbirth, and the
postpartum period, while child health is a state of physical, mental, intellectual, social and emotional
wellbeing and not merely the absence of disease or infirmity (WHO, 2012). Many factors affect
pregnancy and childbirth outcomes, including preconception health status, age of the mother, poverty,
and access to appropriate healthcare during and after pregnancy (Healthy People 2020, 2015).
Assumptions
The study assumed participants voluntarily shared their lived experiences pertaining to the
phenomenon of healthcare access in Cameroon by being truthful in their answers to all interview
questions. I assumed participants spoke English and understood questions during the interview
process. I also assumed that readily available literature on the phenomenon under investigation will
help inform development and implementation of effective policy and program interventions to address
the fundamental causes of healthcare access challenges for this population.
I assumed that creating awareness among this population will increase demand for healthcare,
improved knowledge will change health behavior, and women will access health services such as
prenatal care and have facility-based deliveries if services are available. To avoid the effects of
assumptions on the study, I performed purposive sampling. Through purposive sampling, the creation
of bias was prevented at every stage of the study. The use of purposive sampling targeted the
population under study and helped to reach the targeted sample more quickly.
Scope and Delimitations
This inquiry was limited to the perceptions of Cameroon WCBAs regarding access to
healthcare services. The study focus arose from findings indicating that WCBA in Cameroon,
particularly those in poor rural communities, have limited access to healthcare facilities and services

11
that cater to their healthcare needs (World Bank, 2013). Despite a growing need for a sustainable and
affordable healthcare system that meets the basic healthcare needs of WCBA who need medical care,
a gap persists in understanding the reasons behind inaccessibility issues and how such issues have
influenced the personal satisfaction and health-awareness frameworks that do exist. Although
researchers suggested that the health of WCBA in the southwest region of Cameroon is of great
concern, there was however, limited data about how women in these regions perceive their health and
healthcare access. The lack of information on how WCBA in this region perceive healthcare access is
the rationale for focusing on this study.
The screening process for study participants excluded women under the age of 18, as they are
considered minors and unethical. The study focus was on WCBA in Cameroon 13 to 45 years of who
have experienced childbirth and access to healthcare. Additionally, given the characteristics of the
sample size, it may have been too small or homogeneous to make accurate generalized findings to
other similar population out the scope of this study.
Significance of the Study
This paper has crucial implications for healthcare policy formulators in Cameroon. By providing
information that is pertinent to examining and evaluating the situation of healthcare in different parts
of the country, especially in rural areas, healthcare policy formulators have grounds for revising
standing guidelines, and where necessary, introduce new ones to improve the level of healthcare
services. The second theoretical contribution of this paper was expanding existing literature. As noted
earlier, little research exists on the topic, especially regarding the scope of study. Although there is
research evaluating the status of healthcare delivery in developing countries, little research addressed
the identified target population in Cameroon. This study provided information about this segment of
the population through their lived experiences.

12
Summary
Access to healthcare in most countries in the global south continues to be a challenge and
disproportionately affects WCBAs (Imo et al., 2016). This problem is exacerbated in poor and rural
communities in these countries with limited resources, including Cameroon (Phung et al., 2014).
Despite the growing need for a sustainable and affordable healthcare system that meets the basic
healthcare needs of WCBAs who need medical care, a deficiency of investigation persists regarding
how WCBAs seeking healthcare services perceive healthcare access through their lived experiences
and access of the existing healthcare system in Cameroon.
This descriptive phenomenological study allowed WCBAs an opportunity to express their
opinions about their experiences when seeking healthcare services in Cameroon. Chapter 1 provided
an overview and background of healthcare access for WCBAs in Cameroon, in addition to the problem
and purpose of the study, nature of the study, and research questions. Chapter 1 also explored the
significance of the study, highlighting implications for positive social change.
Chapter 2 will provide a review of the extant literature on Cameroon, access to healthcare, equity of
women’s health status, barriers to healthcare access, maternal and reproductive health, maternal-child
morbidity and mortality among pregnant women, and a summary. Chapter 3 will describe the
methodology for the study, including justification for the phenomenological approach, role of the
researcher, data collection and analysis, and ethical considerations. Chapter 4 will describe the results
of the data collection, including quotations from participants about their experiences and viewpoints.
Chapter 5 will conclude the study, providing an interpretation of the results and suggestions for future
research and practice.

13
Chapter 2: Literature Review
Introduction
The purpose of this qualitative study was to examine how WCBAs seeking physician services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. Also, this study discerned how WCBAs perceive the overall process of access to healthcare
institutions. Examining how WCBAs in Cameroon perceive the quality of the healthcare services
offered and how this impacts their quality of life is significant. Cameroonian WCBAs living in rural
communities are most impacted by lack of services due to poverty, low income levels, lower levels of
education, and poor infrastructure (Kruk et al., 2010). Although the need for improved access to
affordable healthcare services for WCBAs has existed for a long time, little has been documented
regarding the perceptions of this population regarding healthcare access and quality of care.
Cameroon is located in central Africa, with an estimated population of 21.7 million living in
475,442 square kilometers (Nzima Nzima, 2014). The overall region contains 58 districts, 360
subdistricts, and 339 councils (Tandi et al., 2015). Cameroon was ranked 150th of 187 countries on
the Human Development Index in the 2014 Human Development Report, having scored 0.512 on a
scale of 0 to 1; Cameroonians have a life expectancy of 55.5 years (Nzima Nzima, 2014). Specifically,
the country is located at the bottom of the Gulf of Guinea and is surrounded by Nigeria, Chad, Congo,
Gabon, Guinea, and Central African Republic. The public healthcare sector of Cameroon follows the
regional delegations of health and health districts comprising of tertiary, secondary, and primary
healthcare delivery services.
14
Figure 2. Map of Africa describing geographical location and healthcare structure (Egbe, 2014).
Literature Search Strategy
This study used five major library databases to conduct the literature review: ProQuest
Research Library, PsycINFO, PubMed/Medline, Web of Science, and EBSCOHost. The ProQuest
multidisciplinary library database contains peer-reviewed articles that address several subtopics
related to this paper. PsycINFO mainly contains psychology papers. PubMed/Medline is a medical
library database that contains a few articles related to the research. To provide a wider coverage of the
subtopics, I also used the Web of Science database. The EBSCOHost database contains several articles
related to the topic.
I used two search engines to seek relevant articles and publications: Google and Google
Scholar. The Google search engine is considered one of the most effective tools when seeking content
online. Google Scholar is specific for books, patents, theses, dissertations, reports, and peer-reviewed
articles for academic purposes.
Keywords aligned with the subtopics of the study. Where necessary, I used the names of some
authors

15
who specialized in addressing a specific subtopic. The iteration strategy included reorganizing the
keywords, rethinking the phrases, and seeking fresh articles.
Conceptual Framework
As women of Cameroon possess reduced access to healthcare services, access to healthcare
services in Cameroon is an important topic to discuss. No universally accepted definition of the
concept of access to healthcare exists (Jacobs, Por, Bigdeli, Annear, & Van Damme, 2011).
Stakeholders have different approaches to determining the main variables that influence the topic, as
well as different techniques to measure the level of access in different areas. Peters et al. (2008) said
access to healthcare is “the timely use of service according to the people’s need” (p. 161). Peters et al.
used the way healthcare services are delivered to people as an operational proxy for determining the
level of healthcare access. Jacobs et al. (2011) described four main dimensions of access to healthcare:
The availability of the services, the geographic influences that determine accessibility, the cost that
determines the affordability of the services, and the acceptability of the services among the people.
Barriers to access of care can accrue from the demand side, the supply side, or both sides
(Jacobs et al., 2011). Some major barriers on the demand side are culture and tradition. Social
organizations serve as barriers because they are not making efforts to rectify harmful cultural trends
and traditions (Jacobs et al., 2011). Supply side barriers include factors that hinder the relevant
authorities from providing healthcare services to the community (Jacobs et al., 2011). Some of these
include policies that governs the healthcare system and interventions to increase access to healthcare
services.
The concept of access to healthcare has formed the conceptual framework for several studies
that address healthcare planning. Pemunta and Fubah (2015) noted the concept remains elusive despite
efforts to clarify its multiple dimensions and meanings. Researchers must ensure studies avoid
misguiding professionals and policymakers through biased findings (Pemunta & Fubah, 2015). Their
end product is a comprehensive conceptual framework researcher can use to evaluate and plan

16
activities that relate to a society’s access to healthcare services. Some key components of their
suggested framework are a conceptual model that identifies access as a process that is community-
specific. Nonetheless, the concept of access in the field of healthcare essentially denotes the
availability of appropriate healthcare services whenever and wherever needed by the consumer (Obasi,
2013). In the context of women’s health, therefore, access denotes the ease with which women can use
healthcare services whenever and wherever needed (Obasi, 2013).
Generally, factors such as socioeconomic status, availability of healthcare personnel, sociocultural
practices, and the geographic distribution of healthcare facilities determined the degree to which one
gains access to healthcare (Nzima Nzima, 2014). These factors do so by limiting the affordability,
physical accessibility, or acceptability of healthcare services (Bakeera, Wamala, Galea, Peterson, &
Pariyo, 2009). These limitations result in inequitable health outcomes (Gulliford & Morgan, 2003).
For instance, Low-income individuals report poor health outcomes compared those in high-income
groups. Differences in income often lead to differences in health outcomes.
The concept of access closely relates to the concept of equity, especially with respect to controllable
or
remediable health aspects (Gulliford & Morgan, 2003). Equity is about ensuring all individuals and
groups have equal access to quality healthcare services (Eide et al., 2015). Gender is one factor through
which differences in access to healthcare, or the quality of healthcare, are apparent. Gender polarity is
particularly true for developing nations like Cameroon, where women have poor access to basic health
services such as maternal health services (Sheikh et al., 2015). Differences in health outcomes are
even more pronounced among
WCBAs, who have unique health needs. Income levels magnify these differences (Sheikh et al., 2015).
Healthcare access is, therefore, an important indicator of the soundness of a healthcare system.
Equity
Equity in the distribution of healthcare services is another reason for the poor health status of
Cameroon;

17
hence, it is important to discuss equity. Health equity is the principle underlying a commitment to
reduce, and ultimately eliminate disparities in health and in its determinants, including social
determinants. Pursuing health equity means striving for the highest possible standard of health for all
people, and giving special attention to the needs of those at greatest risk of poor health, based on social
conditions (Braveman, 2014). The particular aim of doing this is helping societies focus on physical
health, measured by elements such as mortality and well-being. The need to improve the health status
of the most vulnerable populations drives the importance of equity in health. Disadvantaged groups
across the globe have the least chance of survival when attacked by disease (Whitehead, 2014). In
addition, large gaps in mortality exist between urban and rural populations in various countries. In
many cases, rural populations performed poorly in access to quality healthcare when compared to their
counterparts in urban areas (Whitehead, 2014).
The concept of equity in healthcare has also received a fair share of theoretical adjustments
through the years to guide operationalization and measurement (Braveman & Gruskin, 2003), aimed
at helping achieve a modern society. Braveman and Gruskin (2003) said that “equity in healthcare is
the absence of systematic disparities in health between groups with different levels of underlying social
advantage/disadvantage” (p. 1). The advantages and disadvantages that determine the level of
healthcare include power, wealth, and gender (Braveman & Gruskin, 2003). Other operational
elements that determine differences in equity include racial, ethnic, and religious factors (Braveman
& Gruskin, 2003).
Women’s Health Status in Cameroon
For women, especially those of childbearing age (15–45 years), the significance of access to
healthcare
services cannot be overemphasized. These services range from maternal health services (prenatal,
child birth, neonatal, and postpartum care) to services relating to family planning, reproductive-tract
infections, sexually transmitted diseases (STDs), and gynecological cancers (Obasi, 2013). Without

18
adequate access to these services, women are more prone to complications such as death (of the mother
or infant) during childbirth,
STDs, unwanted pregnancies, and cancers (Obasi, 2013). Lack of access can significantly affect
women’s ability to execute their caregiver roles (Weinger & Akuri, 2007).
Generally, Cameroon has one of the most deplorable healthcare systems in the world, taking the
150th
position of 187 countries in the Human Development Index (Nzima Nzima, 2014). In addition, the
country has a life expectancy of 53 years of age for men and women, and an incidence rate of 24% for
communicable diseases, which is the second highest in the region (World Bank, 2013). Although
measures such as life expectancy and the prevalence of communicable diseases provide valuable
insights about the health status of the general population, they do not consider the significant
differences between the health status of men and women (Obasi, 2013). The patriarchal nature of
societies in Africa places hardships on women that negatively affect their health (Weinger & Akuri,
2007). It is imperative to consider health-status measures specific to women when considering access
to healthcare services. Some measures could include maternal mortality rate, infant mortality rate,
fertility rate, contraceptive prevalence rate, skilled-birth-attendant rate, and frequency of prenatal care
visits.
In Cameroon, the mortality rate for children under the age of 5 is 127 per 1,000 live births (compared
to
107 for Africa and 51 globally), whereas the maternal mortality rate stands at 602 per 100,000 live
births (compared to 480 in Africa and 210 globally; UNICEF, 2011; World Bank, 2011). These high
rates of mortality are often caused by factors such as prepartum and postpartum hemorrhage,
inaccessibility to prenatal and postnatal care, and inadequate access to antibiotics (Obasi, 2013; Tita,
Selwyn, Waller, Kapadia, & Dongmo, 2005). Additionally, skilled healthcare workers do not attend
40% of all births in Cameroon, the contraceptive prevalence rate is below 30%, and a 20% unmet need
persists for family planning (World Bank, 2011). The statistics for skilled birth attendance and unmet

19
need for family planning closely match those of peer developing nations where 45% of women give
birth without trained attendants and 23% of women of childbearing age have unmet family-planning
needs (Obasi, 2013).
Such egregious health indicators clearly showed that access to healthcare is a major challenge
in Cameroon, with women most highly affected. For instance, the high maternal-mortality rate shows
that access to and quality of neonatal and obstetric care remains a major challenge in the country
(World Bank, 2011). Additionally, the low contraceptive rate implies that WCBA are prone to not only
unwanted pregnancies, but also STDs (World Bank, 2011). More importantly, giving birth without
trained attendants implies women are not in a position to manage or prevent likely birth complications
such as postpartum hemorrhage (Obasi, 2013;
Tita et al., 2005). Therefore, it is imperative to consider the factors that hinder access to healthcare by
WCBA.
Barriers to Healthcare Access
Like most sub-Saharan countries, a set of factors hindered equitable access to healthcare in Cameron.
These include poverty, the inadequacy of healthcare personnel and facilities, corruption, low per capita
health expenditure, and sociocultural factors (Business Monitor International, 2014; Ibrahim et al.,
2013; Jacobsen & Nielsen, 2014; Maathai, 2011; Poverty and Health, 2013; World Justice Project,
2013). Poverty is a major challenge in gaining access to healthcare in Cameroon (Commeyras, Ndo,
Merabet, Koné, & Rakotondrabé, 2004; Djomo & Sikod, 2012; Parmar & Agrawal, 2010; Soh, 2007).
According to the World Bank (2011), the country’s poverty rate stands at about 40%, with 33% of the
population living on an income below $1.25 per day. The implication is that an overwhelming majority
of the poor are unable to meet the cost of healthcare. This is particularly true for populations living in
the eastern and northern regions of Cameroon, where the increased inflow of refugees from the Central
African Republic has increased competition for the scarce available basic services (Parmar & Agrawal,
2010; UNICEF, 2011).

20
In most poor countries, poverty is more pronounced among women than men (Weinger &
Akuri, 2007). Cameroon ranks 126 of 157 on the Gender-Development Index (World Bank, 2011).
Additionally, girls enroll less frequently in secondary schools than boys (World Bank, 2011). The
implication is that most women are poor and unemployed, and therefore unable to access quality
healthcare. Studies carried out in Nigeria, Ghana, Uganda, Tanzania, Zambia, and the Democratic
Republic of Congo show that the affordability of healthcare services remains a major challenge for
poor women (Ajaegbu, 2013; Nikiema, Haddad, & Potvin, 2012; Obasi, 2013). Millions of women
around the world, the majority of who are from developing countries, die each year from pregnancy-
and childbirth-related causes (Soh, 2013).
Though disparities in health equity in Cameroon operate across gender, it is important to note
that women are the most affected, lacking education and living in rural areas. A report by the World
Bank (2011) indicates that poor women, those without education, and those living in rural areas, have
a higher fertility rate than women in the highest wealth bracket: those with education living in urban
areas. Poor women generally lack information and education about birth control (Obasi, 2013). Lack
of health information is a major barrier to healthcare access in most developing countries (Sheikh et
al., 2015).
Additionally, the prevalence of mother-to-child HIV transmission, malaria, anemia, and
malnutrition is higher in children whose mothers are poor, compared to those whose mothers are more
socioeconomically privileged (WHO, 2012). The greater prevalence of undesirable health status in
poor women results because poor women are often unable to afford user fees even for highly
subsidized healthcare services (Center for Development of Best Practices in Health [CDBPH], 2012).
For prenatal-care services, for instance, most women are unable to attend the four visits recommended
by the WHO, despite immense subsidization of the services by the government (CDBPH, 2012). As a
result, most women are unable to adopt health practices that minimize maternal and neonatal morbidity
and mortality. Failure to attend prenatal visits also may increase the risk of maternal or infant mortality,

21
because health issues like high blood pressure and STDs are not detected and managed sufficiently
early in pregnancy (Obasi, 2013).
Poor women also have difficulty accessing qualified birth attendants and do not pre-natal visits
(Obasi, 2013), which increases the risk of infant mortality, hemorrhage, and other complications that
may arise because of childbirth. In addition, poverty makes it difficult for women to pay for birth-
control services or transportation to a healthcare facility (Obasi, 2013). Poor women tend to place
health concerns low in life priorities (CDBPH, 2012). Poor sanitation, the lack of access to clean water,
poor housing, and undernutrition further complicate the health status of poor women, increasing the
risk of illnesses such as cholera, typhoid, and malaria (Parmar & Agrawal, 2010; UNICEF, 2011;
Weinger & Akuri, 2007).
Cognizant of the needs of WCBA, particularly those living in rural areas, the Cameroonian
government has recently developed initiatives to enhance their economic power and expand access to
reproductive-health information through the Ministry of Women’s Affairs (McTavish & Moore, 2015;
Soh, 2013). Economic empowerment of women and gender equality are crucial for enhancing
reproductive health and the health of women in general (World Bank, 2011). Empowering women in
poor countries represents a significant prerequisite for any substantial enhancement in the access and
use of healthcare services (Obasi, 2013). With better education, greater participation in the labor force,
and better wages, women will be better placed to access information relating to general and
reproductive health as well as healthcare services. Although the Cameroonian government has
demonstrated commitment to empowering women, gender disparities in economic prosperity in the
country remain.
Another barrier to healthcare access in Cameroon relates to the inadequacy of healthcare
personnel and healthcare facilities (Commeyras et al., 2004; Soh, 2007). Reports indicate that two
doctors service every
10,000 people in Cameroon (Poverty and Health, 2013). This ratio is way below the recommended
minimum of

22
23 per 10,000 for physician-to-population ratio, the country’s health statistics are outside the normal
curve (World Bank, 2013; WHO, 2009). While there is no gold standards for assessing the sufficiency
of the health workforce, World Health Organization estimates that countries fewer than 23 physicians
per 10,000 people will be unlikely to achieve adequate healthcare (WHO, 2009). These statistics are
outside the normal curve because of unsuitable living and working environments; for example, salary
cuts have prompted many public health personnel in Cameroon to either intend to migrate or migrate
to other sectors or abroad for better conditions
(Tandi et al., 2015). Additionally, 40% of all physicians in the country practice in the central region,
where only 18% of the overall population lives (World Bank, 2013). As for maternal health, 1.6 nurses
and midwives service 1,000 people (World Bank, 2011), with the nurse and midwife inadequacy more
pronounced in rural areas (CDBPH, 2012). The implication is that WCBA are unable to access quality
neonatal and obstetric care, thereby increasing the risk of maternal complications and death.
Reports further indicated that 18 healthcare providers service 10,000 people in Cameroon,
which is below the 23 healthcare providers per 10,000 people recommended by the WHO (CDBPH,
2012). The scarcity of healthcare providers is a significant problem in Cameroon and the scarcely
available healthcare facilities in
Cameroon are often short of essential drugs, immunization supplies, beds, and medical-emergency
equipment (UNICEF, 2011). As a result, women often do not get quality prepartum and postpartum
care (Obasi, 2013), exacerbated by limited access to specialty services such as advanced diagnostic
and treatment equipment (Morales, Lara, Kington, Valdez, & Escarce, 2002). With the exception of a
few public Mother and Infant Centers that generally provide services to expectant women and those
with children to the age of 3, Cameroon does not have specialized medical facilities that focus on the
health of women (Weinger & Akuri, 2007). The limited availability of specialized equipment explains
why the majority of women with gynecological cancers (cervical, breast, and ovarian) are diagnosed
when the cancers are at an advanced stage (Ako, Fokoua, Sinou, & Leke, 2015).

23
The inadequacy of healthcare personnel and healthcare facilities is further compounded by long
distances to hospitals and the lack of available transportation, which make it difficult to receive timely
treatment (Morales et al., 2002). Particularly in rural areas, patients often have to travel long distances
before accessing a healthcare facility. A study carried out in the Mamfe region of Cameroon
demonstrated that one- third of respondents attended prenatal visits outside their catchment health area
(Edie et al., 2015). Although the Edie et al. (2015) study may not be representative of Cameroon as a
whole, it clearly demonstrates how the geographical distribution of healthcare facilities in the country
hinders access to healthcare services. Large geographical distances reduce the motivation to attend as
many prenatal visits as required (Edie et al., 2015), and cause women to seek delivery assistance from
traditional birth attendants (Kiguli et al., 2009).
Not only women in Cameroon, but also those throughout sub-Saharan countries – Nigeria,
Zambia, Mali, and Uganda – experience problems of long distances and lack of transportation to
healthcare facilities. (Ajaegbu, 2013; Kiguli et al., 2009; Obasi, 2013; Odetola, 2015). These problems
are exacerbated by climatic factors such as rain, which make the already poor roads impassable due to
flooding or muddiness (Nikiema et al., 2012; Obasi, 2013). Due to such difficulties, individuals may
be deterred from travelling to healthcare facilities, electing instead to make use of traditional doctors
(Obasi, 2013).
The problem of inadequate healthcare facilities and healthcare personnel in most developing
countries, including Cameroon, can be attributed to insufficient government expenditure on healthcare
(Center for Reproductive Rights, 2003). Insufficient government expenditure largely explains why the
few available healthcare facilities have limited qualified healthcare workers and is often short of
essential materials such as drugs, beds, and modern medical equipment. Cameroon has the highest per
capita health expenditure in subSaharan Africa, $61 per person compared to $51 for sub-Saharan
Africa (World Bank, 2013). Nonetheless, government expenditure on health is limited and comprises
about 27% of the total healthcare burden, with the rest financed by citizens and international donors

24
(World Bank, 2013). Limited government expenditure on healthcare often implies that women have to
pay for their healthcare services, presenting a major challenge for women (Nikiema et al., 2012). Due
to the gap left by the government in ensuring equitable access to healthcare, nongovernmental and
religious organizations such as the Cameroon Healthcare Access Program, supported by the World
Justice Project, have continued to play a front-line role in expanding healthcare access in the country
(Nikiema et al., 2012).
The high cost of healthcare services, inadequate healthcare facilities, inadequate healthcare
personnel, and limited budgetary allocation present deterrents to the use of healthcare services. These
problems are exacerbated by widespread corruption in public health facilities, which compels citizens
to pay bribes to access medical services that are supposed to free (World Justice Project, 2013).
Negative personnel attitudes, scolding of women, verbal abuse, slapping of women during labor and
delivery, misdiagnoses, excessive wait times, uncomfortable waiting benches, deplorable hygienic
conditions, and embarrassing physical examinations are common occurrences in public health
facilities (Kiguli et al., 2009; Obasi, 2013). Poor quality of care significantly deters women from
seeking help in public healthcare facilities.
As demonstrated in a study of 26 Cameroonian women by Weinger and Akuri (2007), some women
do
not view public health facilities as an available alternative. In another study that sought to examine
pregnant women’s perceptions of prenatal services in Cameroon’s Mamfe Health district, the
perceived quality of care significantly determined the choice of a prenatal site (Edie et al., 2015). A
related study, though not carried out in Cameroon, reported similar findings (Odetola, 2015). One may
elect not to make a prenatal visit, given the perceived lack of benefit or perceived poor quality of
services provided. In alignment, the health-belief model holds that individuals evaluate the benefit to
be obtained from a healthcare intervention against the financial, physical, and psychological costs
involved in using the intervention (Ajaegbu, 2013). If the perceived benefit outweighs the perceived
cost or barriers, the person uses the intervention, and vice versa.

25
The studies particularly demonstrated that perceptions about public health services can
significantly influence the extent to which women use those services. In contrast, Fotso and Mukiira
(2011) demonstrated that women did use public health facilities extensively, especially those from
low-income backgrounds, despite the perceived poor quality of service they offer. The study result
may indicate that poor women often have no option but to use inadequate public services. Studies
conducted in Uganda, though not specifically in the context of women’s health, reported similar
findings (Bakeera et al., 2009; Kiguli et al., 2009). The influence of perceptions on the use of
healthcare services cannot be ignored.
Perceptions originate not only from economic and health-system factors (such as scarcity of
healthcare facilities and personnel, quality of care, and demographic variables such as income and
educational level; Odetola, 2015), but also religious beliefs and sociocultural practices (CDBPH,
2012). Religion and culture can significantly influence the extent to which one uses healthcare
services, particularly for prenatal services (CDBPH, 2012). Women may ignore prenatal visits due to
beliefs and practices that generally discourage the use of modern medicine. The use of traditional
medicine is common in Cameroon, accounting for about 18% of all sources of health services in the
country (Kamgnia, 2006).
Beliefs and sociocultural practices may also affect the extent to which a woman uses modern birth-
control methods (Obasi, 2013), with strong influences on contraceptive use, particularly in developing
countries
(Obasi, 2013). Catholic and Islamic countries have traditionally condemned contraceptives, thus,
women’s use of contraceptives in these countries continues to be markedly influenced by religion and
culture. In Cameroon, about 53% of the population subscribes to Catholicism whereas approximately
22% are Muslims (Center for
Reproductive Rights, 2003). Additionally, Cameroonian women have 4.41 children on average
(O’Reilly, 2010), which is quite high compared to developed countries, where the average fertility rate

26
is less than two children (Obasi, 2013). Therefore, a possibility exists that religion and custom
influence a considerable proportion of women of reproductive age about contraceptive use.
Opinions of men about contraceptives can also influence the extent to which women use birth
control
(Obasi, 2013). In particular, men’s desire to sire many children, their distrust of modern birth-control
methods, and the perceived inconvenience brought about by contraceptive use may dissuade women
from using contraceptives. Additionally, due to fear of their husbands, women may feel afraid to
inquire about or use contraceptives (Obasi, 2013). Women in most patriarchal societies have less
decision-making authority about contraceptive use (Weinger & Akuri, 2007), thereby increasing the
risk of unwanted pregnancies, STDs (Obasi, 2013), and mother-to-child transmissions of HIV
(Nguefack et al., 2016). In some societies, women must seek the consent of their husbands prior to
visiting a health center, and in some circumstances, may not receive such consent (Nikiema et al.,
2012). Marital status and women’s autonomy in making decisions relating to healthcare can
significantly influence the extent to which women seek healthcare services (Odetola, 2015).
Traditional practices often affect not only the use of contraceptives and prenatal services, but
also women’s physical and psychological health (Weinger & Akuri, 2007). Practices such as female-
genital mutilation, early and forced marriage, and delivering children at home are still pervasive in
many African societies to include Cameroon and exposes women to physical torture, but also to
psychological suffering (Weinger & Akuri, 2007)
Maternal and Reproductive Health
In Cameroon, people survived on less than $2 per day (Abrokwah et al., 2016). The Cameroon
government allocates 6% of its budget to healthcare, which is very low for a population of
approximately 23 million inhabitants (Abrokwah et al., 2016). The fee-based system introduced in
Cameroonian hospitals allows medical facilities to charge fees for treatments and services which has
led to many deaths due to lack of medical care when are unable to pay for services (McTavish &
Moore, 2015; Soh, 2013). Women seeking child birth services and who are unable to do so in the

27
hospitals are sometimes compelled to give birth at home with the help of unskilled matrons, thereby
risking their lives and the lives of their children (Soh, 2013). The 2010 World Bank indicators on
maternal mortality in Cameroon suggest that, 700 out of 100.000 women die of pregnancy
complications or childbirth (World Bank, 2013). Childbirth remains a significant risk factor for
mortality where one woman dies every two hours from pregnancy complications or childbirth, and
one pregnancy out of 127 is fatal (World Bank, 2013). This number is alarming, considering that in
most countries in the global south in 2010, this ratio is much lower (World Bank, 2013).
Globally, WHO (2012) recommended that pregnant women obtain at least four prenatal check-
ups by a skilled birth attendant. However, in developing countries women may not be able to obtain
the recommended services owing to a myriad of social and economic challenges. Cameroon has made
significant improvements in reproductive health-service provision. For instance, the percentage of
healthcare delivery service delivery in Cameroon has increased from 26% in 2008–2010 to 36% in
2015 (Schlegel, 2015). However, maternal and child healthcare-service indicators in Cameroon are
low compared to other countries in the global south. Another study indicated that up to 90.7% of
pregnant Cameroonians do not receive all of the recommended prenatal visits attended by a skilled
provider (Woodsong et al., 2014).
Only 67% of WCBA obtained the recommended four prenatal visits, according to WHO standards,
and
only 35% of pregnant women sought professional childbirth services in clinics during January of 2016
(Fletcher et al., 2016). Some factors attributed to such low use of health services across developing
countries include conformity to cultural norms at the personal and community level and the inadequate
and unequal distribution of health resources (McTavish & Moore, 2015). Notable examples include
personal factors; for example, older women tend to seek traditional childbirth methods that contribute
to the low turnout for maternal-health services (Soh, 2015). In addition, the level of education may
influence the awareness of such individuals, whereas religious inclination tends to keep women from

28
seeking maternal healthcare (McTavish & Moore, 2015; Soh, 2013). In addition to the poverty status
of the country, dire environmental conditions negatively affect maternal–child health.
Maternal–Child Morbidity and Mortality among Pregnant Women
The use of maternal–child health services is important in reducing maternal and child mortality, as is
the
achievement of universal reproductive health-services access. In addition to a high mortality rate of
670 per 100,000 children born (Whitaker et al., 2016), 75% of births are performed outside of clinics
and healthcare facilities, and 15% of pregnant women do not receive any prenatal care (McTavish &
Moore, 2015; Soh, 2013). As a result, most pregnant women risk developing prenatal or at-birth
complications that ultimately end up in
fatalities.
Ajong et al. (2016) conducted qualitative research in northern Cameroon and compared the national
mortality rate among children 5 years or younger with the mortality rates of the population that
received health and other community-development programs, including those receiving care and
services from trained health workers and agents, healthcare providers, and community-outreach
programs. Approximately 3,427 women of reproductive age participated in this study. The researchers
surveyed and interviewed the women about the long-term impact of health and other community-based
programs working to reduce infant mortality. The study revealed that programs that combined
community-health outreach with education and sensitization on health promotion contributed to a
sustainable reduction in mortality of children 5 years and younger (Ajong et al., 2016). Cost remained
a significant barrier to women receiving skilled healthcare during deliveries. Only 6.4% of the poorest
women received care from a skilled attendant at delivery, compared to 67.5% of the richest one fifth
of women (Ajong et al., 2016).
Lack of adequate education leaves most of the Cameroonian population entwined in myths about
health

29
and illness. These myths have caused delayed treatments, and in some cases, caused direct harm
(Ajong et al., 2016). Most pregnant women in Cameroon do not seek prenatal care and deliver with
unskilled matrons. Although these matrons are ill-trained and poorly equipped to respond to
emergencies that arise during labor and delivery, many women entrust their lives, and the lives of their
babies, to them (Ajong et al., 2016).
Childbirth educators should consider birthing-environment risks. For most pregnant women with low
socioeconomic status, Cameroon remains a high-risk environment for infant deliveries. At least one
woman dies every minute from childbirth complications; 20 more suffer infection, disease, and injury
(Ajong et al., 2016).
The largest number of these deaths links to hemorrhage and infection, facilitated by generally poor-
quality care. Deaths and disease can be prevented when women have access to efficient health
equipment, services, and trained healthcare workers. The highest percentage of mother–child deaths
occurs during labor and birth and the immediate post-delivery period, accompanied by sepsis and
excessive bleeding (Ajong et al., 2016).
Across the world, approximately 25% of maternal deaths are due to hemorrhage (Ajong et al.,
2016). The onset of hemorrhage is unpredictable and immediate. Without quick intervention,
hemorrhage can lead to hypovolemic shock, succumbing to mortality. Delays in recognizing postnatal
hemorrhage, delays in transportation to health centers, and delays in medical attendance contribute to
the high maternal-mortality rate (Ajong et al., 2016). Infection is responsible for 15% of maternal
deaths (Ajong et al., 2016). Unhygienic environmental conditions that lead to the high rate of mother–
child sepsis could be prevented by implementing sterile environments in health clinics during birth
(Ajong et al., 2016). Basic birth kits can increase the knowledge of perinatal care, aseptic delivery
practices, and infection prevention. Ajong et al. (2016) showed that when birth kits were used in
perinatal care, women and babies fared better. With the use of these kits, the rate of infection was 13
times less probable (Ajong et al., 2016).

30
Summary
The literature review demonstrated that the perception of access to healthcare varied across
communities. Perhaps the most significant factors determining access are economic and social
influences. Clearly, the Cameroon government has taken steps to improve the level of access to
healthcare; however, factors such as the country’s socioeconomic organization and regional
differences in development hinder equal access to quality healthcare. The reviewed works showed that
the level of access to healthcare in Cameroon was below global standards, and key players in
healthcare provision in the country include the government, churches, and traditional formats.
Some key themes emerging from the literature reviewed were women’s perceptions of
governmentsponsored healthcare, the role played by traditional healers, and differences in
socioeconomic development. Few studies addressed these key themes and it is not clear what role they
play in determining the level of access to healthcare by WCBA in Cameroon. The identified gap in
knowledge therefore is the perception of access to healthcare among these women, as influenced by
the identified factors.
This study was designed to fill the identified gap in knowledge. Previously, most information
accrued
from quantitative research studies. This study was qualitative and aimed to answer the research
questions, how do WCBA seeking healthcare services in Cameroon perceive the process of healthcare
access through health institutions? How do WCBA seeking healthcare services in Cameroon perceive
the quality of healthcare services offered through healthcare institutions? How do WCBA seeking
healthcare services in Cameroon understand the impact of healthcare services on their quality of life?
Overall, the study helped determine perceptions of access to healthcare for a vulnerable target
population, WCBA, in Cameroon. Chapter 3 described the methodology used to gather data. Chapter
3 covered justification for the phenomenological approach, role of the researcher, data collection and
analysis, and ethical considerations. The chapter ended with a summary.

31
Chapter 3: Research Method
Introduction
The purpose of this qualitative study was to examine how WCBAs seeking physician services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. The study explored how WCBAs perceive the overall process of access to healthcare

32
institutions. Examining how WCBAs in Cameroon perceive the quality of the healthcare services
offered and how this impacts their quality of life is significant. The research methodology outlined in
this chapter discerns the target population’s perceptions regarding access to healthcare. In this chapter,
I highlighted the methodology I used to address the problem and the purpose of the study. The research
design and rationale, research questions, justification of the phenomenological approach, and role of
the researcher are also explored. I defined the participant selection criteria, instrumentation, data
collection and analysis, and strategies for addressing credibility, transferability, dependability, and
ethical considerations.
Research Design and Rationale
This study was qualitative in nature, seeking to understand the perceptions of Cameroonian
WCBAs regarding access to healthcare. Through a qualitative study, the meaning of the phenomenon
and the experiences of the identified population and their views regarding the issue were the focus.
For this purpose, the approach can be described as “a technique which seeks to describe, decode,
translate and come to terms with the meaning of naturally occurring phenomena in the society” (al-
Busaidi, 2008, p. 175). Phenomenological study research questions aim to uncover and obtain a
detailed understanding of the participants’ lived experiences of the phenomenon under investigation
(Hageman & Frederick, 2013). The following three research questions guided the study and were
critical to understanding the perceptions of WCBAs in Cameroon:
RQ1: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the process
of
healthcare access through health institutions?
RQ2: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the quality
of
healthcare services offered through healthcare institutions?
RQ3: How do WCBAs seeking maternal/child healthcare services in Cameroon understand the
impact
of healthcare services on their quality of life?

33
Justification for the Phenomenological Approach
For this investigation, I used phenomenological techniques to identify specific factors
influencing the phenomenon and characterized the phenomenon by investigating how they perceived
it. The phenomenological approach is important for studying social perceptions, enabling the
collection of deep opinions and insights through constructive means (Smith, 2015). Opinions and
insights are inductive and qualitative, thereby helping establish perspectives. By applying a
phenomenological approach, the experience of the larger population can be studied with high degrees
of accuracy by bracketing a representative sample. This approach builds on a paradigm of personal
knowledge (Smith, 2015); therefore, the validity and reliability of the findings could address the
central objective of the study.
Some specific strengths of the phenomenological approach made it suitable for this study. Most
significantly, the approach enabled the collection of information that is rich in facts, detailed, and
relevant to the human experience (Smith, 2015). Through a critical examination of raw data, it was
possible to determine how WCBAs in Cameroon perceived their current access to healthcare, and
understand how the system affected these women personally and collectively.
Role of the Researcher
Although the role of the researcher is to ensure that the data collected and presented has high
validity, it
is almost impossible to rule out bias. In qualitative studies, bias is the aspect of research that affects
the validity and reliability of the findings (Hibberts & Johnson, 2012). I made concerted efforts to
avoid prejudices and preconceptions, remained objective, and had an open mind when interviewing
participants. Using the reflexivity technique allowed me to address any biases and to remain objective
(Hibberts & Johnson, 2012). Asking the right questions to participants, interviewing the right people,
using appropriate data collection methods, and appropriately interpreting data collected minimized
potential bias in this study.

34
Moderator bias is one of the risks to research validity and reliability. Moderator bias is enabled
by facial expressions, body language, and mode of communication, all associated with the
establishment of rapport between the researcher and participants (Smith, 2015). My personal opinion
was avoided through purposive sampling by applying reflexivity to ensure preconceptions and
perceptions do not influence the overall research process and finding. The other identified significant
bias was biased answering. This aspect is characterized by untrue and partial reporting by participants
(Hibberts & Johnson, 2012). This form of bias was outside the control of the researcher.
Methodology
Participant Selection
I recruited 10 participants from the town of Mamfe, located in the southwest region of
Cameroon. Mamfe is a rural area, located outside the major cities and towns. The system of care serves
smaller populations, has fewer available resources, and provides more healthcare services through
faith-based and nonhealth-related partners and organizations (Varda, Hardy, Millar, & Talmi, 2016).
Qualitative phenomenological studies should contain a sample size between 15 and 20 participants
(Marshall, Cardon,
Poddar, & Fontenot, 2013). For special cases, the size can be slightly higher until a saturation level is
achieved (Marshall et al., 2013). Participants were limited to 10 due to the fewer number of WCBAs
willing to participate and meet the inclusion criteria. Inclusion criteria were that participants were
between 18 and 45 years of age who lived in the town of Mamfe and were able to read, understand,
and speak basic English. WCBAs in Cameroon range from 13 to 45 years of age, but for ethical
reasons, I excluded women under the age of 18, as they are considered minors.
After receiving approval from the Walden Institutional Review Board with IRB #12-17-18-
0325173, I sought permission from the Mamfe, Cameroon local council, and the pastor of the Mamfe
cathedral to recruit study participants. After obtaining permission from the mayor and pastor, I
distributed flyers (see Appendix A) in church on Sundays, where women congregate to worship, and

35
on market days, where women sell and buy food products. I posted flyers in these locations to increase
the chances of more participants seeking to participate in the study. In order to make the source of
contact easier, a local telephone number was included in the flyer.
The participants interested in the study were educated and briefed on the background of the study as
well as include their right to participate or not to participate in the study. I informed participants that
their participation was voluntary and based on informed decisions. Participants were also informed
that they may not have any direct benefit for participating in the study. However, each participant was
compensated $10, or equivalent to roughly 5000 CFA for participating in the study. During the
prescreening sessions, the participants provided me with detailed information, including the times that
they were available for the interview. I scheduled interviews with participants who were eligible and
interested at a date and time convenient for them in a designated office located in a community hall in
Mamfe.
After initial eligibility screening of participants (see Appendix B), I scheduled a face-to-face
interview, which was the primary method of data collection. I greeted participants when they arrived
and established a relationship in an attempt to gain their trust. Participants were asked to sign a consent
form to take part in the study. I sought permission from participants to record the interview process. I
completed the demographic information sheet (see Appendix C) prior to beginning the interview. To
establish accuracy in my methodology and data collection instrument (see Appendix D), I interviewed
the first two participants as a pilot study. This pilot study allowed me the opportunity to minimize
redundancy when the saturation point was reached, test interview questions to allow for accurate data
collection, and practice interviewing. I briefed participants about the nature of the research. Use of the
reflexivity technique helped to remove bias from the research and presented true results.
Pilot Study
In order to establish accuracy of the methodology and data collection instrument (see Appendix D), I

36
interviewed the first two participants as a pilot study. The pilot study helped in testing the quality of
the methodology. A pilot study is a small-scale study through which the researcher can evaluate the
feasibility, effective size, adverse events, time and cost of research (Whitehead, Sully, & Campbell,
2014). Pilot studies also provided an opportunity of testing interview questions and interviewing
practice.
Instrumentation and Data Collection
I collected data by conducting semi-structured interviews. Interviews are the most common
techniques
used to collect qualitative information (Sarantakos, 2012). The duration of each interview ranged from
45 to 60 minutes. Interviews took place in a designated office located in a community hall for privacy
at a time convenient to participants. Participants were allowed to openly share their perceptions about
the current healthcare system of Cameroon.
The goal of semi-structured interviews was to explore and probe interviewee’s responses to obtain an
understanding of the phenomenon under study (Creswell, 2013). This process of interviewing focused
on details of the interviewee’s life experiences and social behavior. Creswell (2013) noted that during
interviews, the interviewer attempts to engage the interviewee in a conversation about attitudes,
interests, feelings, concerns, and values as they relate to the research topic. I recorded the contact
information for participants for the purpose of following-up. Member checking technique allowed
participants the opportunity to review their statements for accuracy after the interview to increase the
credibility of the study (Harper & Cole, 2012).
To participate in the study, participants met the following criteria: Be a woman of childbearing age
(18–45 years), live in the rural community in Mamfe in the southwest region of Cameroon, and be
able to write, read, and speak basic English.
Data Analysis
NVivo 11 and the Colaizzi seven-step process for phenomenological data analysis were used for data
37
organization and analysis. The seven-step process focused on defining concepts and categories (Tesch,
2013). QSR NVivo 11 allowed me to classify, sort and arrange information, and examine relationships
in the data collected (QSR International, 2013). The qualitative data from the interviews were grouped
into themes. The themes were developed based on the objectives identified in the first chapter. The
themes emphasized informants’ responses to particular items in the interviews, and how the issues
they raised related to the objectives of the research.
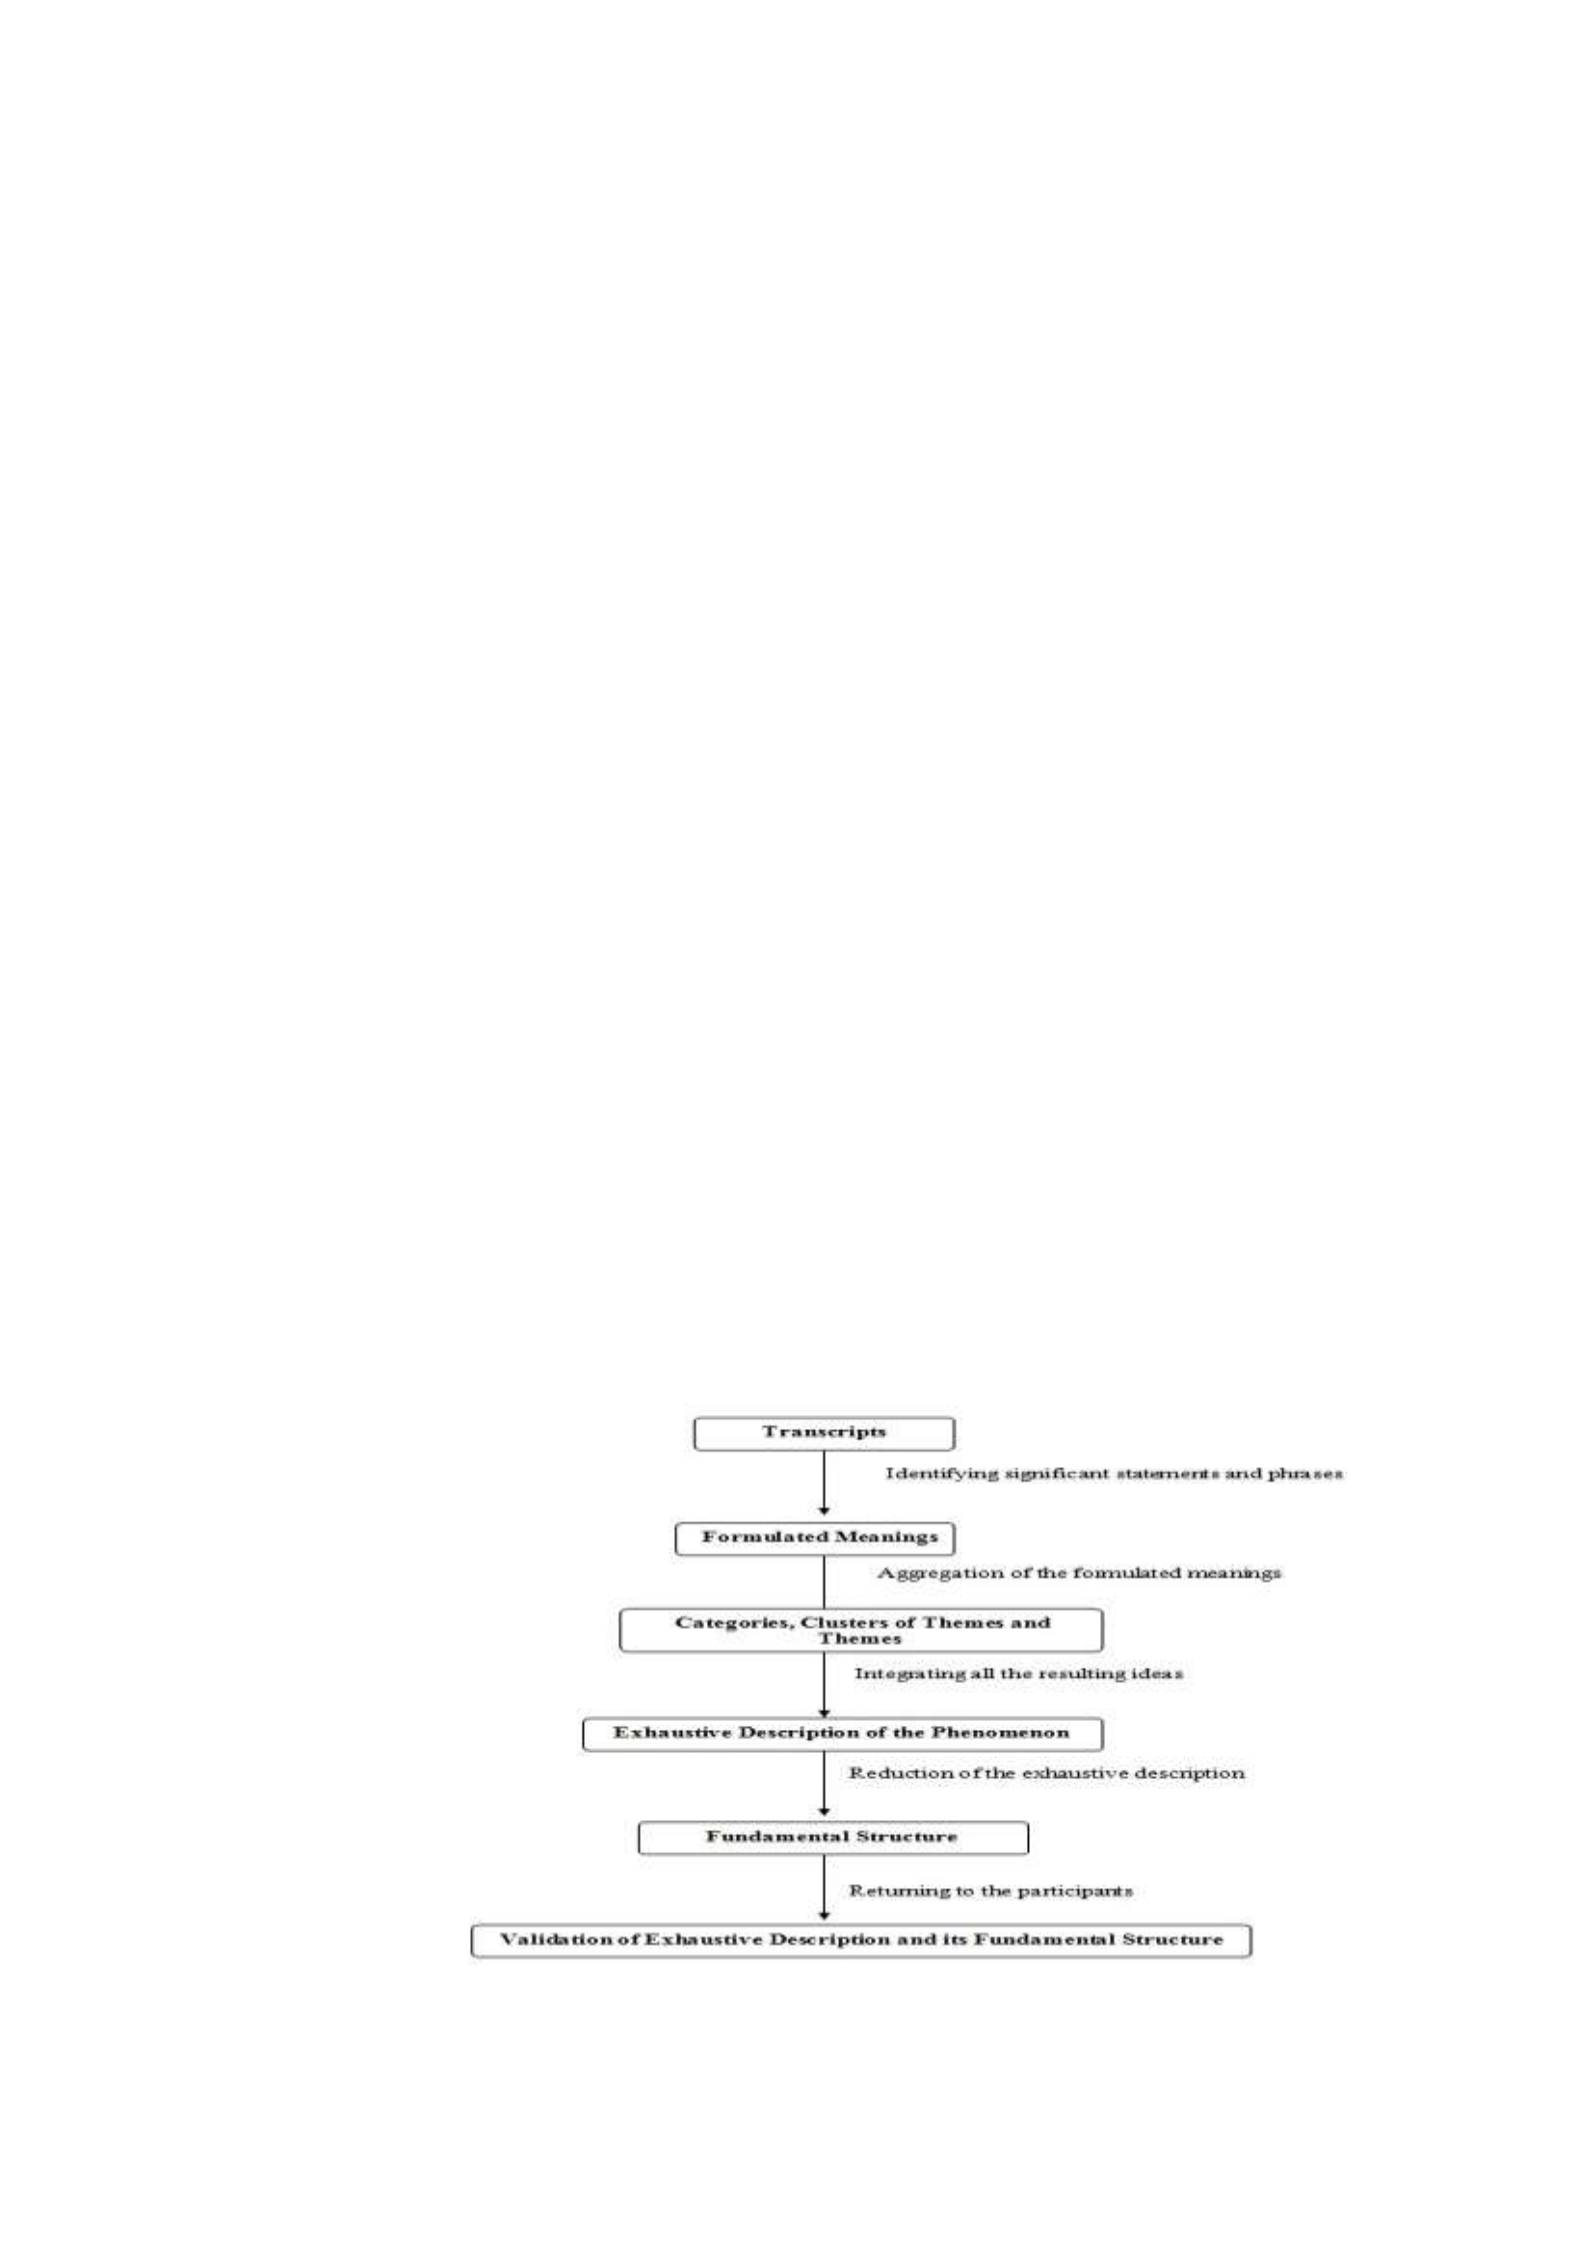
According to Shosha (2012), using the Colaizzi seven-step process for phenomenological data
analysis allows for comprehensive description and analysis of the phenomena under research. This
study used the Colaizzi process for phenomenological data analysis (as cited in Shosha, 2012) as
follows: I read and re-read each transcript and obtained general knowledge about the content, I
extracted significant statements that pertain to the phenomenon under study from each transcript, I
recorded these statements on a separate sheet, indicating the pages and line numbers, formulated
meanings from these significant statements, sorted these formulated meanings into categories, clusters
of themes, and themes. I integrated study findings into an exhaustive description of the phenomenon
under study, described the fundamental structure of the phenomenon, and sorted validation of the
findings from the research participants to compare the researcher’s descriptive results with
their experiences. (Shosha, 2012; see Figure 3).

38
Figure 3. A summary of Colaizzi’s strategy for phenomenological data analysis. Note. Adapted with
permission from “Employment of Colaizzi's strategy in descriptive phenomenology,” by A. G. Shosha
(2012), European Scientific Journal, 8(27), 34. Copyright 2012 by European Scientific Institute.
Issues of Trustworthiness
To ensure transferability, the external validity of the research was addressed. According to Polit and
Beck, (2013), this is the extent to which the findings of a study can be applied in other situations. This
enabled a more inclusive and overall picture of the topic to be painted. The outcomes of the study were
checked to ensure that they will not be treated in isolation when used by other researchers. All the
processes within the investigation were reported in detail. This enables the works of future researchers
who may follow this paper’s process to be a prototype model. Additionally, all elements of the process
were covered in detail so that other researchers can understand the steps that have been followed.
The first step to ensure the credibility of the study was learning the participant’s culture prior
to data collection. This was achieved through consultations with the mayor of Mamfe rural council
and pastor of the cathedral and also using medical reports and journal information. Through these
ongoing consultations I obtained adequate understanding of the community and its inhabitants.
Second, the pilot study used to test the quality of the interview guide was helpful to ensure credibility.
According to Chenail (2011), the pilot study is a method of testing the quality an interview
guide/protocol for identifying any potential researcher biases and to determine if the intended
procedure performed will be achieved.
To ensure confirmability and dependability, the research methodology was applied throughout the
research process. Confirmability of the research process ensured that the instruments used were not
dependent on human skills and perceptions (Polit & Beck, 2013). To ensure dependability, it is
important that the findings of the investigation were a result of the experiences of the target population
and their independent ideas (Polit & Beck, 2013). It is also important to ensure that the results were
not due to personal opinions. The detailed methodological description of this study helped the reader
of the paper to determine the extent to which the data is constructed and the level of its acceptance.

39
This process was aided by an audit trail, which enables the audience of the study to trace back the
process and make meaning out of the procedures (Polit & Beck, 2013).
Ethical Considerations
For this study, I obtained legal consent to conduct the study from the Walden University’s
Institutional Review Board approval # 12-23-15-0406456. I obtained legal consent from the
Institutional Review Board prior to conducting the study and from the jurisdiction where research was
conducted. Participants completed and signed a consent form demonstrating understanding of the
purpose of the research and allowing researcher to interview them. The main ethical concern for the
study was informing participants about the nature of the study, and having them to agree to participate
in the data-collection exercise.
I kept data collected from the field safely in a locked cabinet in my home office. I stored the
digitally recorded data using a secured computer protected by a password. I included only the
processed and analyzed data in the discussion chapter of this paper and no raw data was shared. After
a post-study period of 5 years, I will destroy hard copies of the raw data by shredding and will
permanently erase the soft copies (in flash drives and other electronic media).
Summary
This chapter outlined the methodological approach for the study. The general aim of the
methodology was to present a systematic process through which relevant data was collected. The study
was a qualitative investigation using descriptive phenomenological techniques to collect field data.
The number of participants were 10, comprising women of 18 to 45 years of age. The data was
collected through face-to-face interviews and was analyzed using NVivo 11 and the Colaizzi seven-
step process to identify themes and subthemes. Interviews were conducted in an office located in a
community hall in the community and the nature of interviews were semi structured. In Chapter 4 the
detail of the demographics of study participants, data collection, study setting, and results were

40
discussed under identified themes in order to explore the impact and perceptions of Cameroon women
about the healthcare services’ quality and access.
Chapter 4: Results
Introduction
The purpose of this qualitative study was to examine how WCBAs seeking physician services
perceive healthcare access through their lived experiences and access to the existing healthcare system
in Cameroon. Also, this study attempted to discern how WCBAs perceive the overall process of access
to healthcare institutions. Examining how WCBAs in Cameroon perceive the quality of the healthcare
services offered and how this impacts their quality of life is significant. The following research
questions were addressed through comprehensive semistructured phenomenological face-to-face
interviews with 10 women of childbearing age regarding their perceptions of access to healthcare in
Cameroon:
RQ1: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the process
of
healthcare access through health institutions?
RQ2: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the quality
of
healthcare services offered through healthcare institutions?

41
RQ3: How do WCBAs seeking maternal/child healthcare services in Cameroon understand the
impact
of healthcare services on their quality of life?
This chapter includes information relating to the pilot study that follows the main study, study
setting,
demographics of the participants, data collection, data analysis, and study results. This chapter also
includes information pertaining to research quality and trustworthiness.
Pilot Study
I completed a pilot study after receiving approval from the IRB and updating the study flyer (see
Appendix A) and interview guide (see Appendix D) with IRB #12-17-18-0325173. Two participants
were
recruited to take part in the pilot study to ascertain the reliability of the data collection instrument and
quality of the methodology. The pilot study participants were similar demographically to the main
study participants and were treated the same in all ways. Although data from the pilot study is not
usually used in the main study, they were included in this study due to the limited number of WCBAs
willing to participate and meeting the inclusion criteria and because the pilot study participants had no
revisions to the questionnaire (see Appendix B).
The pilot study participants met all eligibility criteria detailed in the study invitation flyer. I screened
participants using the initial eligibility screening tool, and I requested participants to complete a
demographic data form. At the start of the interview, I read the consent form to each participant and
obtained their signature as an indication of full approval and consent to participate in the pilot study.
The two pilot study participants (Megan and Maria) answered all interview questions with responses
that clearly addressed the three research questions. After completion of eligibility screening, I noticed
none of the potential study participants have a first name beginning with an ‘M’. To ensure
confidentiality, I randomly assigned names to participants beginning with the letter M (Madelene,
Margaret, Maria, Martha, Mary, Megan, Melissa, Mercy, Miriam, and Molly).

42
Participants’ responses from the interview confirmed that the study flyer, demographic form,
eligibility screening tool, and consent form aligned with the problem and purpose of the study. It was
telling that participants understood all the study documents, since they did not ask for further
clarification during the recruitment and interview process. Completing the pilot study further enhanced
my interviewing skills, increased my confidence, and prepared me for the main study interviews.
Research Setting
The study took place in Mamfe, located in the southwestern region in Cameroon. I conducted
face-toface interviews with each participant in an office in a community hall to maintain privacy and
ensured participants were comfortable. Prior to the date of the first interview, a member of the Mamfe
rural council gave a tour of the council building and I was introduced to a few staff members present.
My visitors were allowed to use a small waiting area in the lobby with comfortable chairs and a small
coffee table. The council member briefed the receptionist about the study. On the day of the interview,
the receptionist received participants and I was notified by phone of their arrival.
The interview room was small yet, comfortable with a round table and four chairs. I welcomed
participants and allowed them the opportunity to pick a seat of their choice. Prior to the interview, I
spent a few minutes interacting with participants to create rapport and make them feel comfortable
and relaxed. I gave participants $10 (5000 CFA) as indicated in the study flyer and let them know they
did not have to complete the interview before they were compensated. Participants were offered water
and a snack. They proceeded with filling out the demographic checklist and signed the consent form.
I began to administer the interview questions using the interview guide with the participants’ consent.
At the end of each interview, I thanked the participant for participating in the study and escorted them
out of the room.
Participant Demographics
Ten women volunteered to participate in the study. Four of these women, Madelene, Maria, Martha,
and
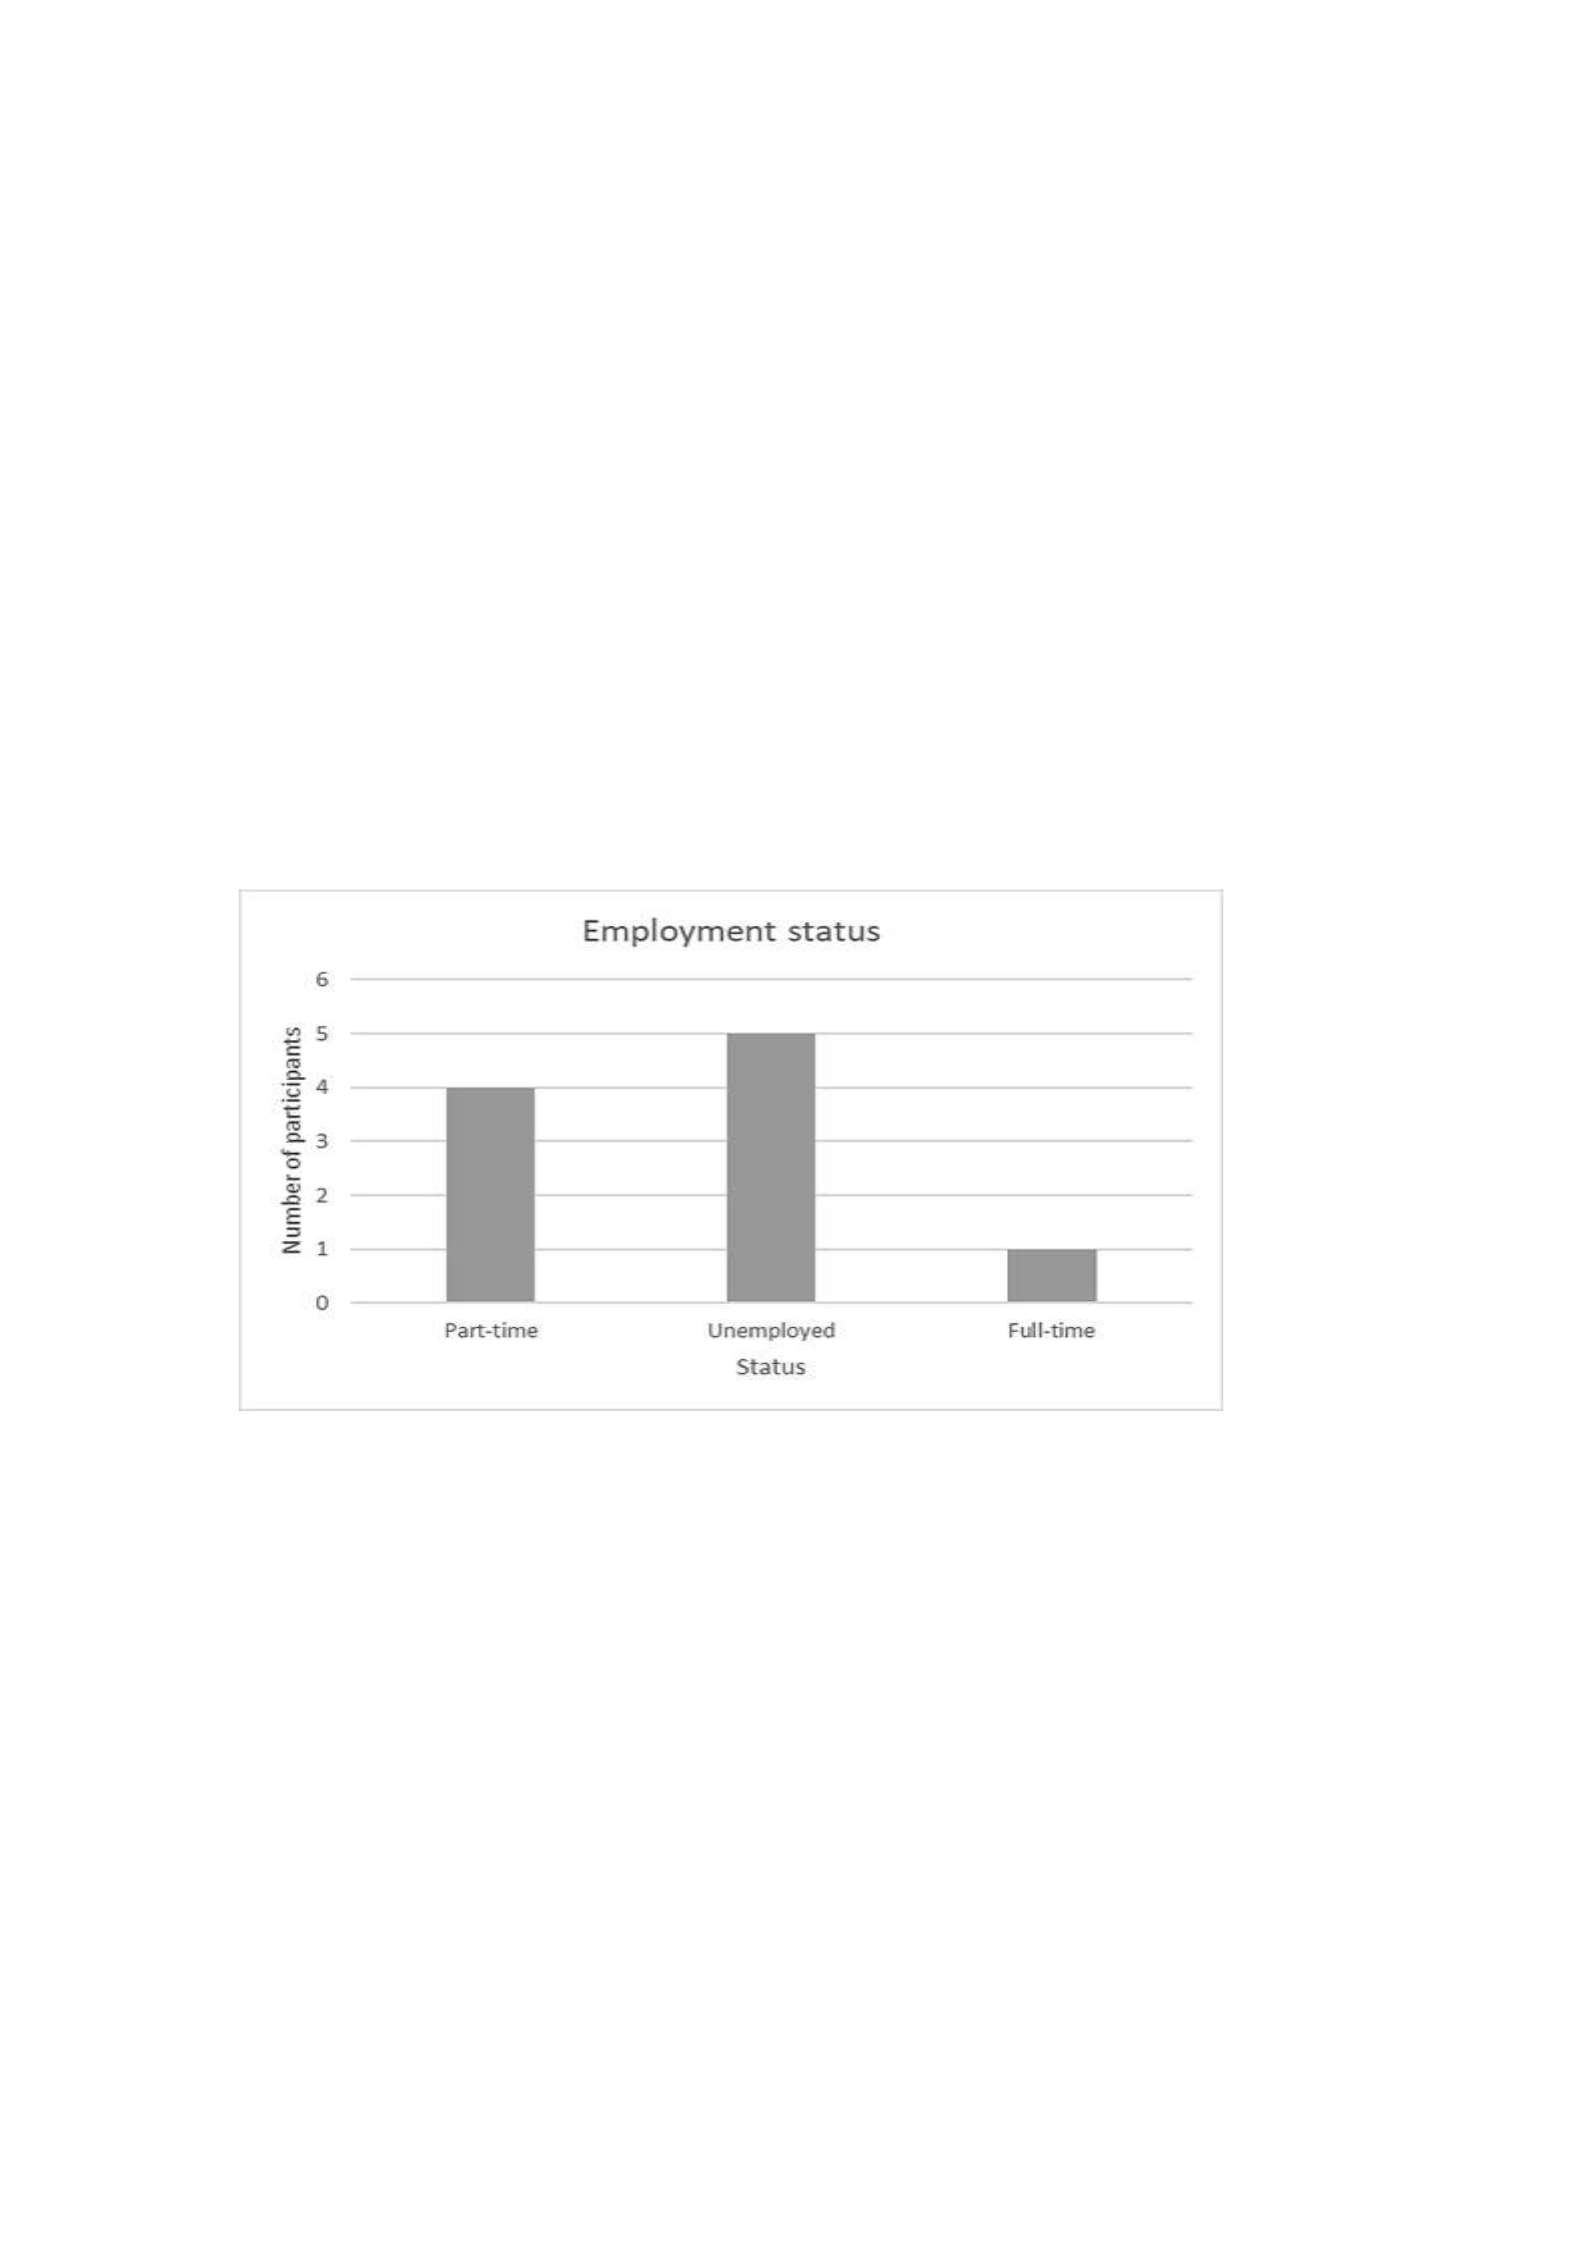
43
Molly, were between 18 and 25, Mary, Meghan, Melissa, Mercy and Miriam were between 26 and 35,
while Margaret was between 36 and 45. Four participants, Madelene, Martha, Melissa, and Mercy,
had less than a high school education, while Margaret, Maria, Mary, Miriam and Molly had a high
school diploma, and Meghan had an associate degree. Nine participants self-rated themselves as low-
income, while Margaret identified herself as having a midlevel income. Five participants were
unemployed (Madelene, Maria, Martha,
Megan, and Mercy). Miriam worked full time, and Molly, Melissa, Mary, and Margaret worked part-
time. Molly was legally separated, Madelene, Maria, Megan, and Mercy were married, and Margaret,
Martha, Mary,
Melissa, and Miriam were not married.
Figure 4. Employment status of the participants.
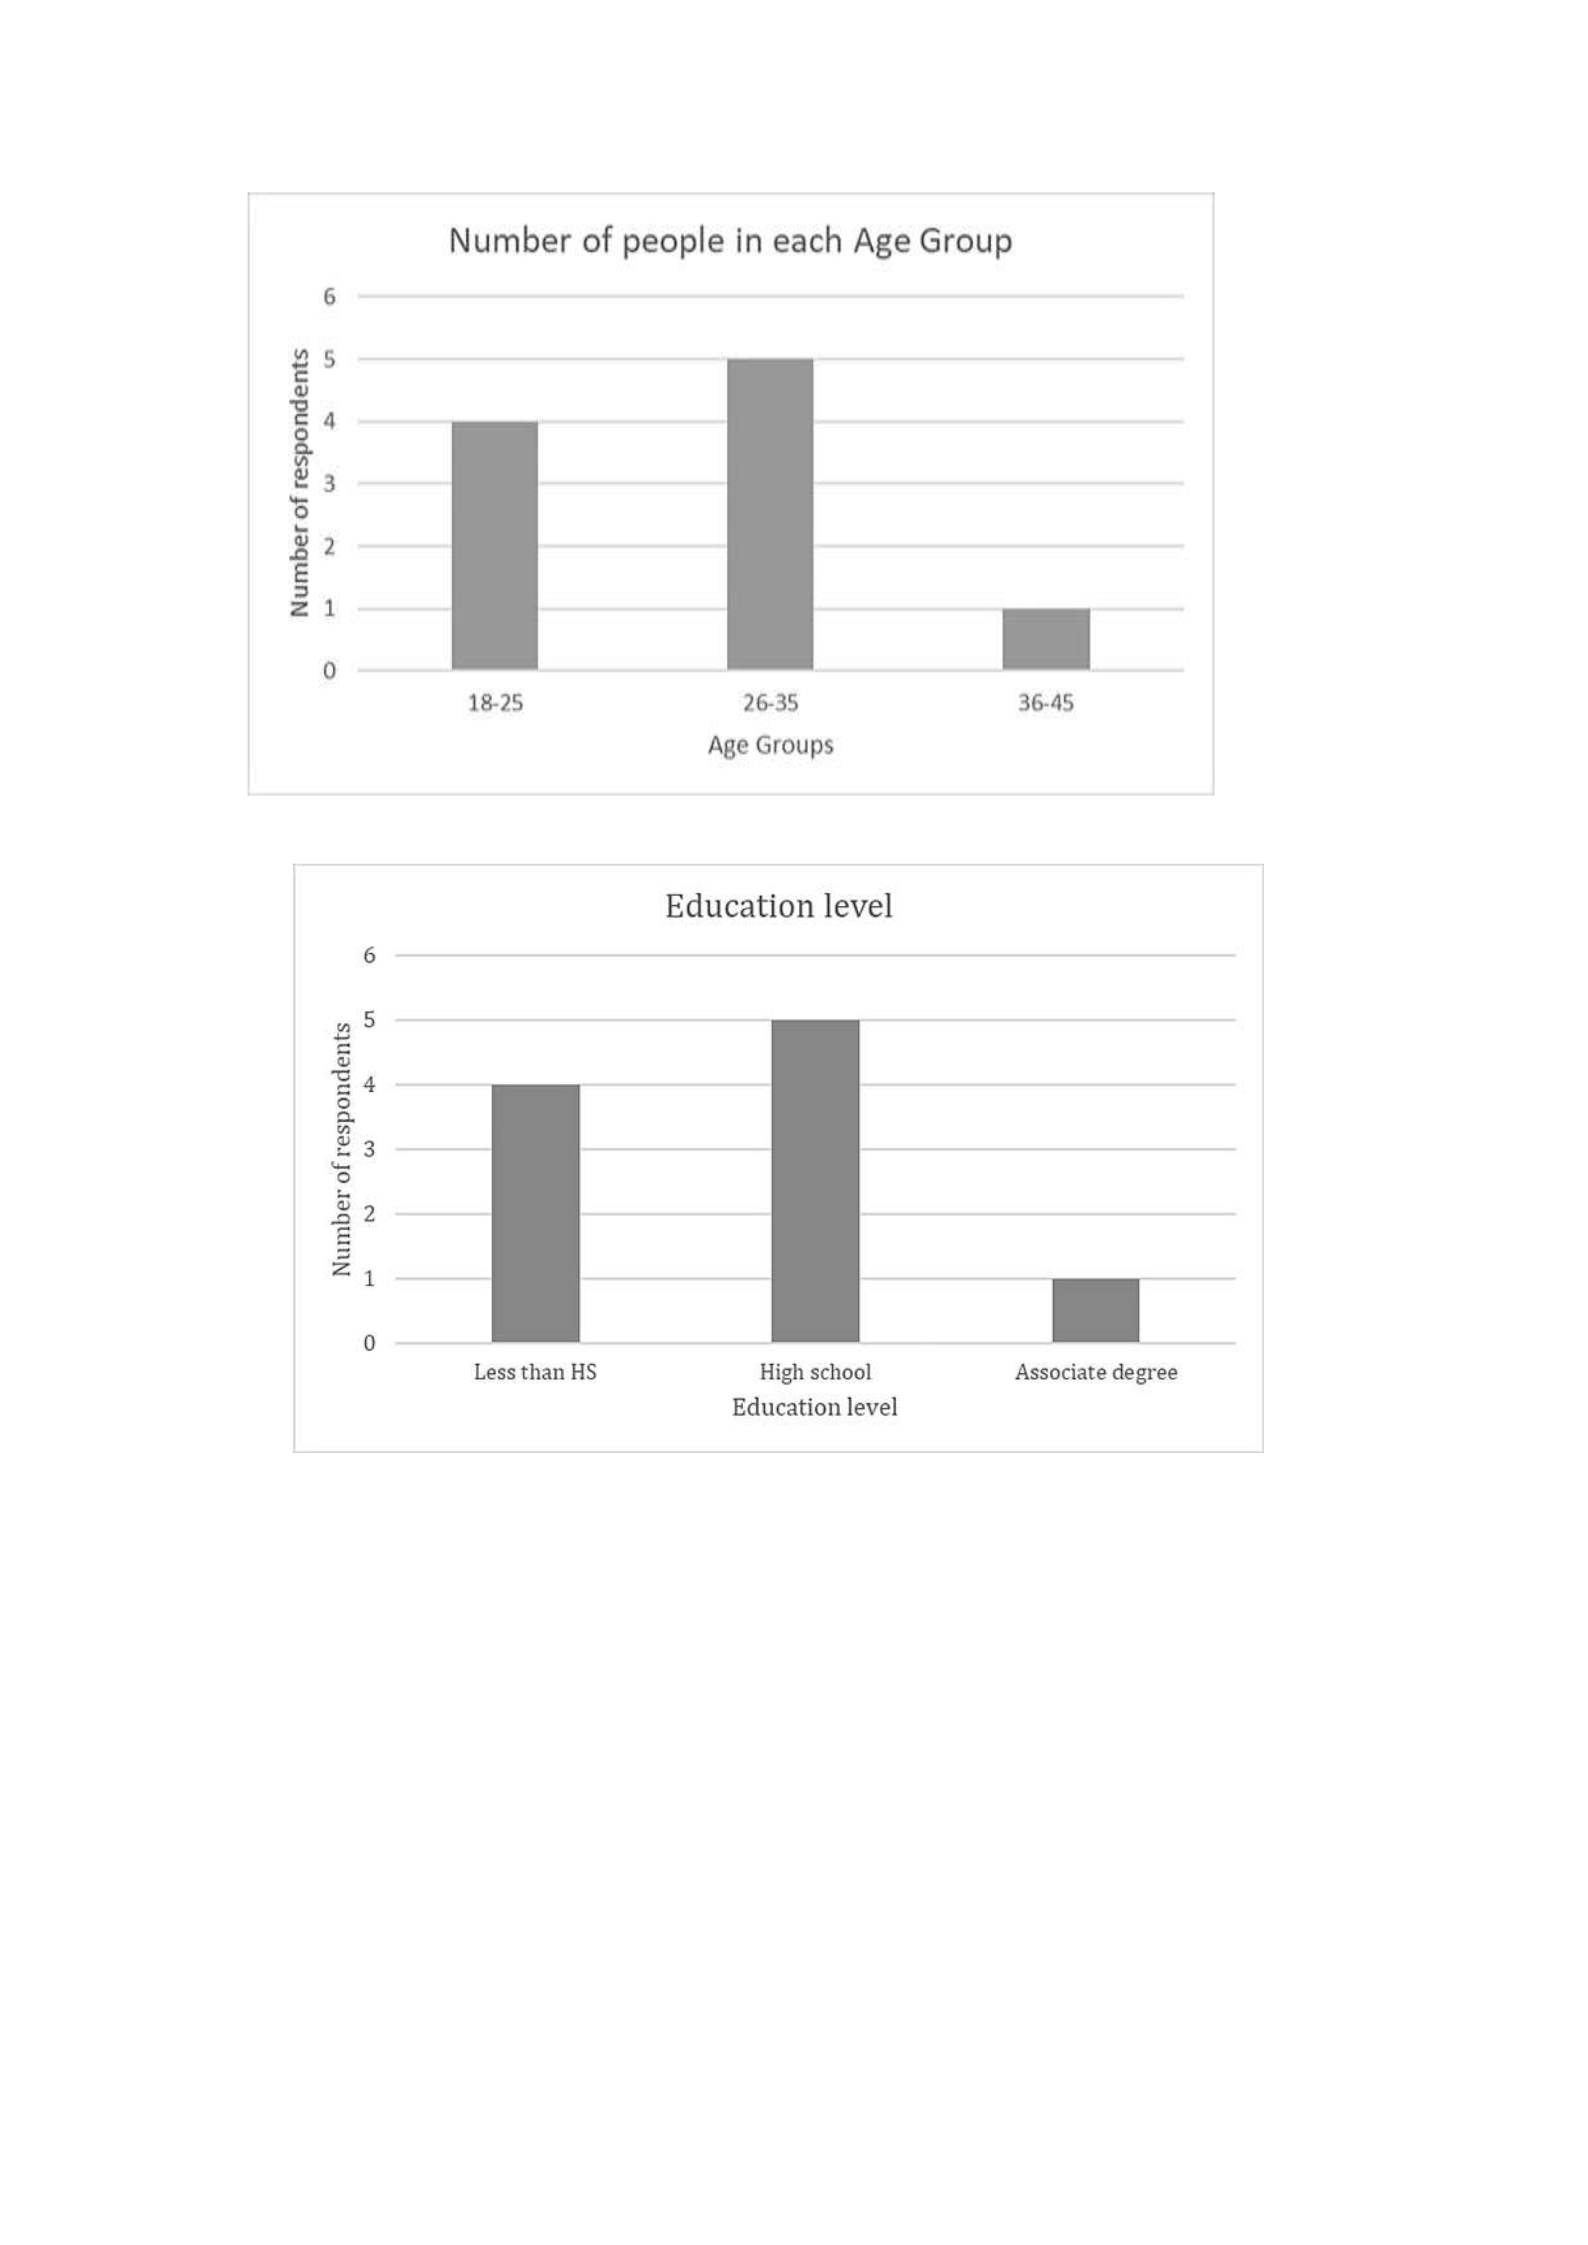
44
Figure 5. Number of participants in each age group.
Figure 6. Number of participants in each education level.
Data Collection
Data were collected from 10 women of child bearing age. These women volunteered their time
and experiences in answering questions outlined on the interview guide (see Appendix D). The
interviews took place between 12/20/2018 and 01/04/2019. The researcher held semistructured
interviews with individual participants in an office in a community hall. The interview sessions lasted
45 to 60 minutes. Participants interested in participating in the study went through the initial screening

45
to ensure eligibility was met. I scheduled a face-to-face interview with participants at a date convenient
for them.
To ensure there was no breach of confidentiality, I immediately downloaded all recorded
interviews from the recording device in a folder on my computer protected by a password. To prevent
data loss, I also saved interview data on an external hard drive protected by password. I transcribed
interview recordings into word document using the same computer to enhance data security. The
recording device and all notes are stored in a locked cabinet in my home office.
Evidence of Trustworthiness
Member checking was used to establish the credibility of the data. The researcher contacted the
participants after the data collection period to check and confirm that the data were indeed what they
had said during the interviews. The pilot study used to test the quality of the interview guide was
helpful to ensure credibility. As posited by Chenail (2011), the pilot study is a method of testing the
quality of an interview guide/protocol for identifying any potential researcher biases and to determine
if the intended procedure performed will be achieved. The researcher constructed an audit trail during
the research process and was always aware of personal biases that may have influenced the study
To ensure transferability, the external validity of the research was addressed. According to Polit
and Beck (2013), this is the extent to which the findings of a study can be applied in other situations.
This enables a more inclusive and overall picture of the topic to be painted. The outcomes of the study
were checked to ensure that they will not be treated in isolation when used by other researchers. All
the processes within the investigation were reported in detail. This enables the works of future
researchers who may follow this paper’s process to be a prototype model. Additionally, all elements
of the process were covered in detail so that other researchers can understand the steps that have been
followed. Recruiting WCBA living in rural areas and those who spoke, wrote and understood Basic
English was designed to enhance transferability of findings to similar populations. However, limits to

46
transferability exist including the education and income level of patients, insurance coverage and
public health usage.
Main Study Findings
The responses from all 10 participants were analyzed using NViVo 11 qualitative analysis tool and
following the Colaizzi seven-step process. The themes generated were shortage of doctors and nurses,
distance to the hospital too far, inadequate money for transport to the hospital, long wait times to see
a doctor or nurse, poor patient outcomes, death of mother/child, paying for healthcare, inaccessibility
of healthcare staff, healthcare access during the last hospital visit, understanding of healthcare access,
understanding of impact of care on quality of life, physical environment of the hospital, unsatisfactory
patient care, shortage of medical equipment or supplies, shortage of healthcare providers, poor
communication by healthcare staff and unprofessionalism by healthcare providers.
The themes shortage of doctors or nurses, long wait times to see a doctor/nurse and inaccessibility
of
doctors or nurses were grouped together under “inadequate healthcare provider team” theme, which
was refined to “timeliness of care and patient Experience with Healthcare Providers,” to reflect a
healthcare quality metric. Shortage of medical equipment or supplies and unsanitary physical
environment were grouped together to form “unsatisfactory medical provision environment” theme,
which was refined to “patient safety” because it is a healthcare quality metric. The codes distance to
the hospital too far and inadequate money for transport to the hospital were grouped into a theme
named transport challenges. The code paying for healthcare was modified to inadequate healthcare
financing to form a theme. The codes poor communication skills, unsatisfactory patient care and
unprofessionalism by healthcare providers were grouped into one theme hostile hospital environment.
The code poor patient outcomes was defined into a theme “patient outcomes and safety” while the
code death of mother or child was defined as maternal and child mortality theme. Figure 7 below is a
word cloud of most frequently used words emerging from the interview responses.

47
Figure 7. Word cloud showing the frequency of the responses.
Table 1
Development of Codes into Themes and Subthemes
Codes
Themes
Subthemes
Long wait times to see a
doctor/nurse and
inaccessibility of doctors
or nurses.
Shortage of medical
equipment or supplies
and unsanitary physical
environment.
Distance to the hospital
too far and inadequate
money for transport to
the hospital.
Paying for healthcare.
Poor communication
skills, unsatisfactory
patient care and
unprofessionalism by
healthcare providers.
Patient outcomes and
death of mother or child.
Timeliness of Care and Patient
Experience with Healthcare
Providers.
Transport challenges
Inadequate healthcare financing
Hostile hospital environment
Patient Outcomes and Safety
Inadequate
healthcare provider
team.
Unsatisfactory
medical provision
environment.

48
Research Question 1: Perception of Process of Healthcare Access
Theme 1: Transport Challenges
Patients encountered transportation challenges when trying to get to the hospital. For example,
Martha
said that there was a day she was “feeling terrible with my pregnancy and had no means of
transportation to the hospital.” She had to endure the pain that day and “only went to hospital on my
scheduled day for antenatal visit.” Money to pay for transportation was often a challenge. Martha said
“It is hard for me personally because transportation to the hospital was usually very hard due to lack
of money.” Ongoing treatment procedures imply increased transportation costs. Megan said “For me
personally, it was hardship in the most part to afford transportation seek treatment.” Other patients live
too far from the hospital. Mary said “The distance to the hospital is far from my home and if I do not
have money for transportation, I will have to walk to the hospital which sometimes takes several hours
depending on my health condition.” Megan once missed an appointment due to transport challenges.
She said “I live far away from the hospital and sometimes difficult to find a vehicle to transport me to
the hospital.” Mercy added “…To find transportation to take you to the hospital is always a challenge
because I do not live close to the road.”
There are consequences when patients cannot access the hospital due to transport challenges.
According to Madelene, “Since there was no money to pay for transportation, I had to trek which is
quite a distance. By the time I got to the hospital, I was told that the doctor is not available and that I
should come back another day.” Mary had to self-medicate as she said “family member bought me
some medication from a local pharmacy which helped a little.” Melissa added “my child had very high
fever and I had no money to transport him to the hospital. However, I used cold water to reduce the
temperature.” Lastly, Miriam had no childcare for the other twin when one of them fell sick and

49
“…could not take him to the hospital because there was no one to stay home with the other child. I
used local treatment (herbs) by the help of a neighbor to stabilize him.”
Theme 2: Inadequate Healthcare Financing
Paying for healthcare is a limiting factor in accessing healthcare. Madelene said “Sometimes you are
required to do blood work which cost money and if you do not have the money, the treatment will be
incomplete.” Margaret added “It was hard for me due to economic hardship. I always struggled when
my child or myself fall sick to seek treatment. Struggled to raise money for transportation to the
hospital, consulting and buying medications.” Martha added “I often find it very difficult to gain
access to a doctor and sometimes unable to afford the medications prescribed.” All patients agreed that
lack of money affects their access to healthcare. Mary said that “If you do not have money, you will
not be treated…. If you are poor, the more you stay in line seeking treatment, the likelihood you may
not be seen by a nurse or a doctor.”
Patients self-medicated when they do not have money to go to a hospital. Maria said “My child got
very sick and I had no money to take him to the hospital. I bought medications from a roadside
pharmacy to manage the situation. Mercy added “Financial hardship is always the aspect that hinders
me sometimes for my child or myself to consult with a doctor. There were a few instances where I was
sick and treated myself both locally with herbs and also buying medications from a local pharmacy….
The system needs to change or else a lot of people will continue to die because of neglect. If you are
poor, you suffer the consequences.” Other consequences are death as Molly indicated “In order for the
doctor to attend to you, you have to have the full amount of money before they can attend to you even
in an emergency situation. If you do not have money, you can easily die because no one will even look
at you or attempt to treat you without money.” Theme 3: Hostile hospital environment.
All participants perceived the hospital environment to be hostile, and the patient care they received
was unsatisfactory in most cases. First, the healthcare providers had poor communication skills and
were rude, uncaring or shouted to patients. Mercy had never had a pleasant experience when consulting

50
with a nurse and gave an example of a humiliating situation she suffered under a nurse “In one of those
visits when I was pregnant, a nurse cursed me out when I was complaining of pain. She told me “did
I put the child in stomach?” Everyone in the waiting area at the lobby started laughing at me. It was
very humiliating and I will never forget that day.” She concluded that “nurses are not friendly and
have poor communication skills.” Later, she added that consulting with a nurse “…always cause me
more pain because of poor communication.” Madelene wondered whether healthcare providers are
paid well because “they often get angry when you consult and not very nice.” Later she added, “Most
staff will ignore you when you ask questions or seeking help.” Prompted for additional comments,
Margaret suggests customer service training for healthcare providers implying they may have poor
communication skills. She said “The doctors and nurses need more training on customer services. If
the Cameroon government can develop training programs to help them improve in their interactions
and relationship with patients, it will be very helpful.” Martha said “…the nurses are generally not
very caring and will shout at you when talking. I am familiar with it and so, not surprising to me.”
Later, she indicated that she has to “ignore their shouting to avoid further confrontation.” Miriam
added “Most nurses were very rude which I was not surprise. I was use to it because that is how they
have always been. The doctors on the other hand spend very little time to check my sick child despite
the very long wait time.” Miriam and Molly said that, some nurses were friendly and did their best to
take care of their children but others “were rude when communicating” while others “not so
concerned.”
Healthcare providers were also unprofessional in some cases and gave care to patients based on wealth
or social status. Maria said “I noticed that the doctors saw patients based on their economic and social
status. If you are rich and have influence in the society, you stand a better chance to be seen by the
doctor at all times and receive better care. If you are poor like me, you may not see the doctor at all.
The healthcare system works well for the rich than the poor.” Mary said although she had encountered
a few “nice” nurses, “…majority lacked good customer service…They see patients based on their

51
economic and social status. If you are wealthy and influential or your parents are influential in the
community, they will definitely get you in for check-up sooner.
They will also treat you nicely.” Later, she also said “If you are poor, the more you stay in line seeking
treatment the likelihood you may not be seen by a nurse or a doctor.” Madelene said that even when
the wait time is so long, “…often times people who came behind you will be called in first because
the nurse knows them.” Margaret added “Sometimes I feel like they do not care if your situation is
critical. They will consult with patients they know first or those who are wealthy.”
Besides treating patients based on class or influence, some healthcare providers treated patients in a
demeaning unprofessional manner. For example, Mary gave an example of something that happened
to her “…In one of my visits, a nurse wrote a prescription that was very expensive and when I tried to
question, she screamed at me and at the same time throwing my hospital book at me.” In other cases,
nurses were involved in selling medications meant to be given to patients. According to Miriam,
“…Some of them will focus more on trying to make extra money by selling their own medications.
Not sure where they get the medications from but
I was told by others that these are medications provided by some philanthropic organizations to help
patients.”
In some instances, patient care was unsatisfactory. Maria received poor care. She said “While at the
hospital, I did everything for myself despite my condition. When I called the nurse for help, she told
me she does not have time for that. I will got up and struggled by myself to get water to shower. The
nurses were not very friendly and nice.” According to Miriam, some nurses have been using one
syringe on more than one patient. She said “…I observed a nurse using one syringe (needle) on two
patients which was mind blowing. You have to be very vigilant when having an injection because a
nurse could use a used syringe on you causing other illnesses.” Madelene said “In the most part, the
nurses are very rude and do not seem to care about the patients. They will scream when
communicating. There was one occasion my child vomited while at the hospital and the nurse
screamed at me stating “You need to clean that mess immediately”. Later, she exemplifies this by

52
saying “when my baby need care after delivery, I will have to scream for help before someone will
come” and prompted for additional comments she added “most nurses and doctors are not very caring
by neglecting patients. They need to show love and compassion.” Maria added that “…the nurses came
across as not caring at all. I had some concerns with my baby and went to them several times to come
and check the baby but no one showed up until the following day. They are usually loud when they
communicate.” About her experience interacting with healthcare providers, she added, “The nurses do
not understand what a patient is going through. The way the nurse reacted when I arrived in the hospital
bleeding indicated to me, she had no idea what she was doing. I did not see the doctor until when I
was about to be discharged. Access to healthcare services needs serious improvement.” Mary gave
examples of when she received poor care. In one instance, “…I was told to wait in the sitting area. I
sat there for almost 2 hours and when I ask the nurse why it is taking so long, she got upset and told
me the doctor is not available and that I should go and come at another date. I finally saw the doctor a
month later.” In her most recent hospital visit when delivering her child, she said, “…it was a difficult
pregnancy and I was very sick. I was admitted in the hospital for 4 days without seeing the doctor….
I had no food for a while because the nurses would not even offer or ask if you are hungry.”
Research Question 2: Quality of Healthcare Services
Theme 4: Timeliness of Care and Patient Experience with Healthcare Providers
Patients have to wait longer before they can be seen by a doctor and sometimes, a nurse and this has
significant consequences on the quality of healthcare they receive. Megan said “The wait time at the
lobby was really disturbing to me considering my condition. It was very uncomfortable, and nurses
did not seem to understand how inconvenient and the pain I was going through.” Later, she added
“The wait time before finding a bed and finally seeing a doctor to begin treatment was very
disappointing. I was very sick and expected to have been placed on a bed sooner…. I felt the care was
not very good. I felt I was neglected for some time.” Melissa added “I went to the Mamfe general
hospital when I was sick with fever. It was a little frustrating for me because with my condition, it still

53
took the doctor very long to attend to me.” Miriam describes her last hospital visit “…I came in with
a lot of pain and sat at the waiting room for some time since there was a long line [of patients].”
Madelene added “The hospital is too small and lots of people waiting in line for treatment which takes
a while for a nurse to attend to you.” The long hours of waiting could be attributed to the shortage or
unavailability of healthcare providers. Most participants including Madelene, Maria, Melissa, Maria,
and Mercy agree that there is a shortage of doctors and nurses. According to Madelene this “…made
it difficult to receive care when you need it in a timely manner.” The few doctors available are too
busy to see patients and delegate the duty to nurses, who are also overwhelmed or see patients for an
inadequate amount of time.
Madelene exemplifies this situation “I consulted with a nurse for all my visits. There was one time I
requested to see a doctor and I was told the doctor is over booked already. I was also told by the nurse
that my condition is not such that requires to see a doctor.” Margaret consulted with a doctor only
when there was a complication. She said “I consult with a doctor only with complications such as
having a C-section when my child was bridged.” Maria added “I saw a nurse when I arrived at the
hospital and that is the only nurse I saw until I left. I was told that the doctor only sees patients in an
emergency situation.” Nurses may prescribe medication when doctors are not available as Mary
illustrates “The doctor was not available on all three occasions I went to the hospital… the nurses
could not really help me because they confessed, they do not have the expertise to take care of my
sickness. However, medications were written to be filled at a local pharmacy.” Unavailability of
doctors has consequences for healthcare delivery as Meghan illustrated “When I was rushed into the
hospital, I was in pain and exhausted. I sat in the hospital lobby for sometime because the doctor was
not available and the nurse did not know what to do.”
Sometimes both nurses and doctors were not available, postponing healthcare access as Melissa
showed

54
“…when I went to the hospital to consult and there was no doctor or nurse to attend to me and I had
to go back home and returned to the hospital the following day.” Later, she added “The fact that it is
always difficult to see a doctor is troubling to me especially if you have a condition requiring a doctor’s
professional advice.” Mercy said there was only one doctor and “…it is difficult to consult with a
doctor... Unfortunately, if you are poor you may never seen a doctor.”
Untimely care and poor patient experience with accessing healthcare particularly due to
inaccessibility and shortage of doctors and healthcare providers influenced the perceived quality of
healthcare negatively.
Theme 5: Patient Safety
The shortage of medical equipment or supplies and unsanitary physical environment compromised
patient safety. The study participants complained of a shortage in medical supplies. Martha, Mary,
Madelene and Meghan all confessed that the hospital they visited lacked adequate medical supplies.
Mary said, “The lack of equipment and basic medical supplies is a huge problem needing attention.”
In instances of shortage, patients may be asked to purchase them as Mary said “…basic items such as
wound dressings, syringes, bandages etc. are not available. They will tell you to go get these items
before they can treat you. There was a lot of concern about nurses using one syringe for multiple
patients.”
In addition, the participants complained about unsanitary physical conditions in the hospital. Mary,
Molly, Melissa, and Madelene all described the hospital as being “unsanitary.” Mary said “…the
hospital environment is not clean enough and needs improvement” while Melissa added “the sanitary
condition definitely needs improvement as you could smell bad odor” and the infrastructure is in “bad
shape.” Miriam added that although the nurses took care of her child, she was not “…very comfortable
with the hospital environment. The hospital was not that clean and had a terrible smell.” In addition,
lighting is a problem as Molly said “Sometimes there are no lights and we have stay in the dark. The

55
generator they have is not very effective.” Unsanitary conditions in the hospital and shortage of
medical supplies may compromise patient safety and thus, influence the quality of healthcare.
Research Question 3: Understanding the Impact of Healthcare Services
The participants seemed to understand the impact of healthcare services as shown in Figure 5. The
following themes emerged from the discussion:
Theme 6: Impact on Patient Outcomes and Safety
Melissa observed that the rudeness and negligence exhibited by nurses may “slow down the healing
process.” She shares how poor patient care impacted her health and led to negative outcomes “…the
medication prescribed for infection did not work at all. Had a doctor seen me, the outcome of my
illness would have been entirely different. I suffered a great deal of pain for the next several days
before I was able to resolve the infection problem with a new medication.” Margaret understood the
impact of healthcare services on patient outcomes and safety. She outlined the importance of maternal
and child care by saying that if “… mother and child are not consulting with a doctor or nurse when
they are sick and if the doctor/nurse do not attend to them soon enough when they are sick, it may lead
to worsening of the condition and ultimately death. Margaret also gave an example of a case where a
lack of immediate attention by the healthcare staff threatened her child’s health. She said, “…In 2017
I took my daughter to the hospital when she had high fever and there was doctor/nurse to attend to her
for several hours. The wait time led to her having a convulsion.” Meghan said “Every human being
deserves basic healthcare services. Specifically, if women and children are unable to gain access to
this basic healthcare services, it could aggravate their current condition leading to complications and
possible death.” Molly summarized this by stating that “Good health requires…being able to go to the
hospital to seek treatment when you are sick. If you cannot take care of your baby and yourself, the

56
situation gets worse and could cause life. Limited finances to provide for their medical care.” The
patients understood the impact of healthcare services on their health outcomes and safety.
The patients explained the impact healthcare services had on maternal and child mortality. Madelene
understood that poor case can cause loss of lives. She defined poor care as “…a doctor or a nurse not
taking time to check the baby or the mother to figure out what their conditions are.” She added that
“The shortage of doctors and nurses and lack of money for hospital visits could worsen a health
situation and ultimately causing lives.” Maria also said her life was at threat at one point due to
negligence. She said “…I was bleeding and the nurse that received me showed no sympathy and did
nothing for several hours. I thought I was going to die.” Martha acknowledged that failure to attend
hospital when she is sick can harm her health. She said “With the economic hardship making it difficult
to go to the hospital when needed could really cause a major health problem down the road.” She gave
an example of when she missed an appointment due to lack of money for transport “…it could have
aggravated my sickness if not of the traditional medication. Therefore, without basic healthcare
services, it could worsen health condition leading to death.” Mary added “The fact that there is lack
of basic items to care for patients, using one syringe for more than one patient and dirty environment
could impact quality of care. It could cause the death of a child or a mother.” Meghan witnessed an
unfortunate case of death due to poor healthcare access. She said, “I have observed in some occasions
where a pregnant woman died with a baby in her tommy because she did not have money for C-section
and the doctor refused to treat her.”
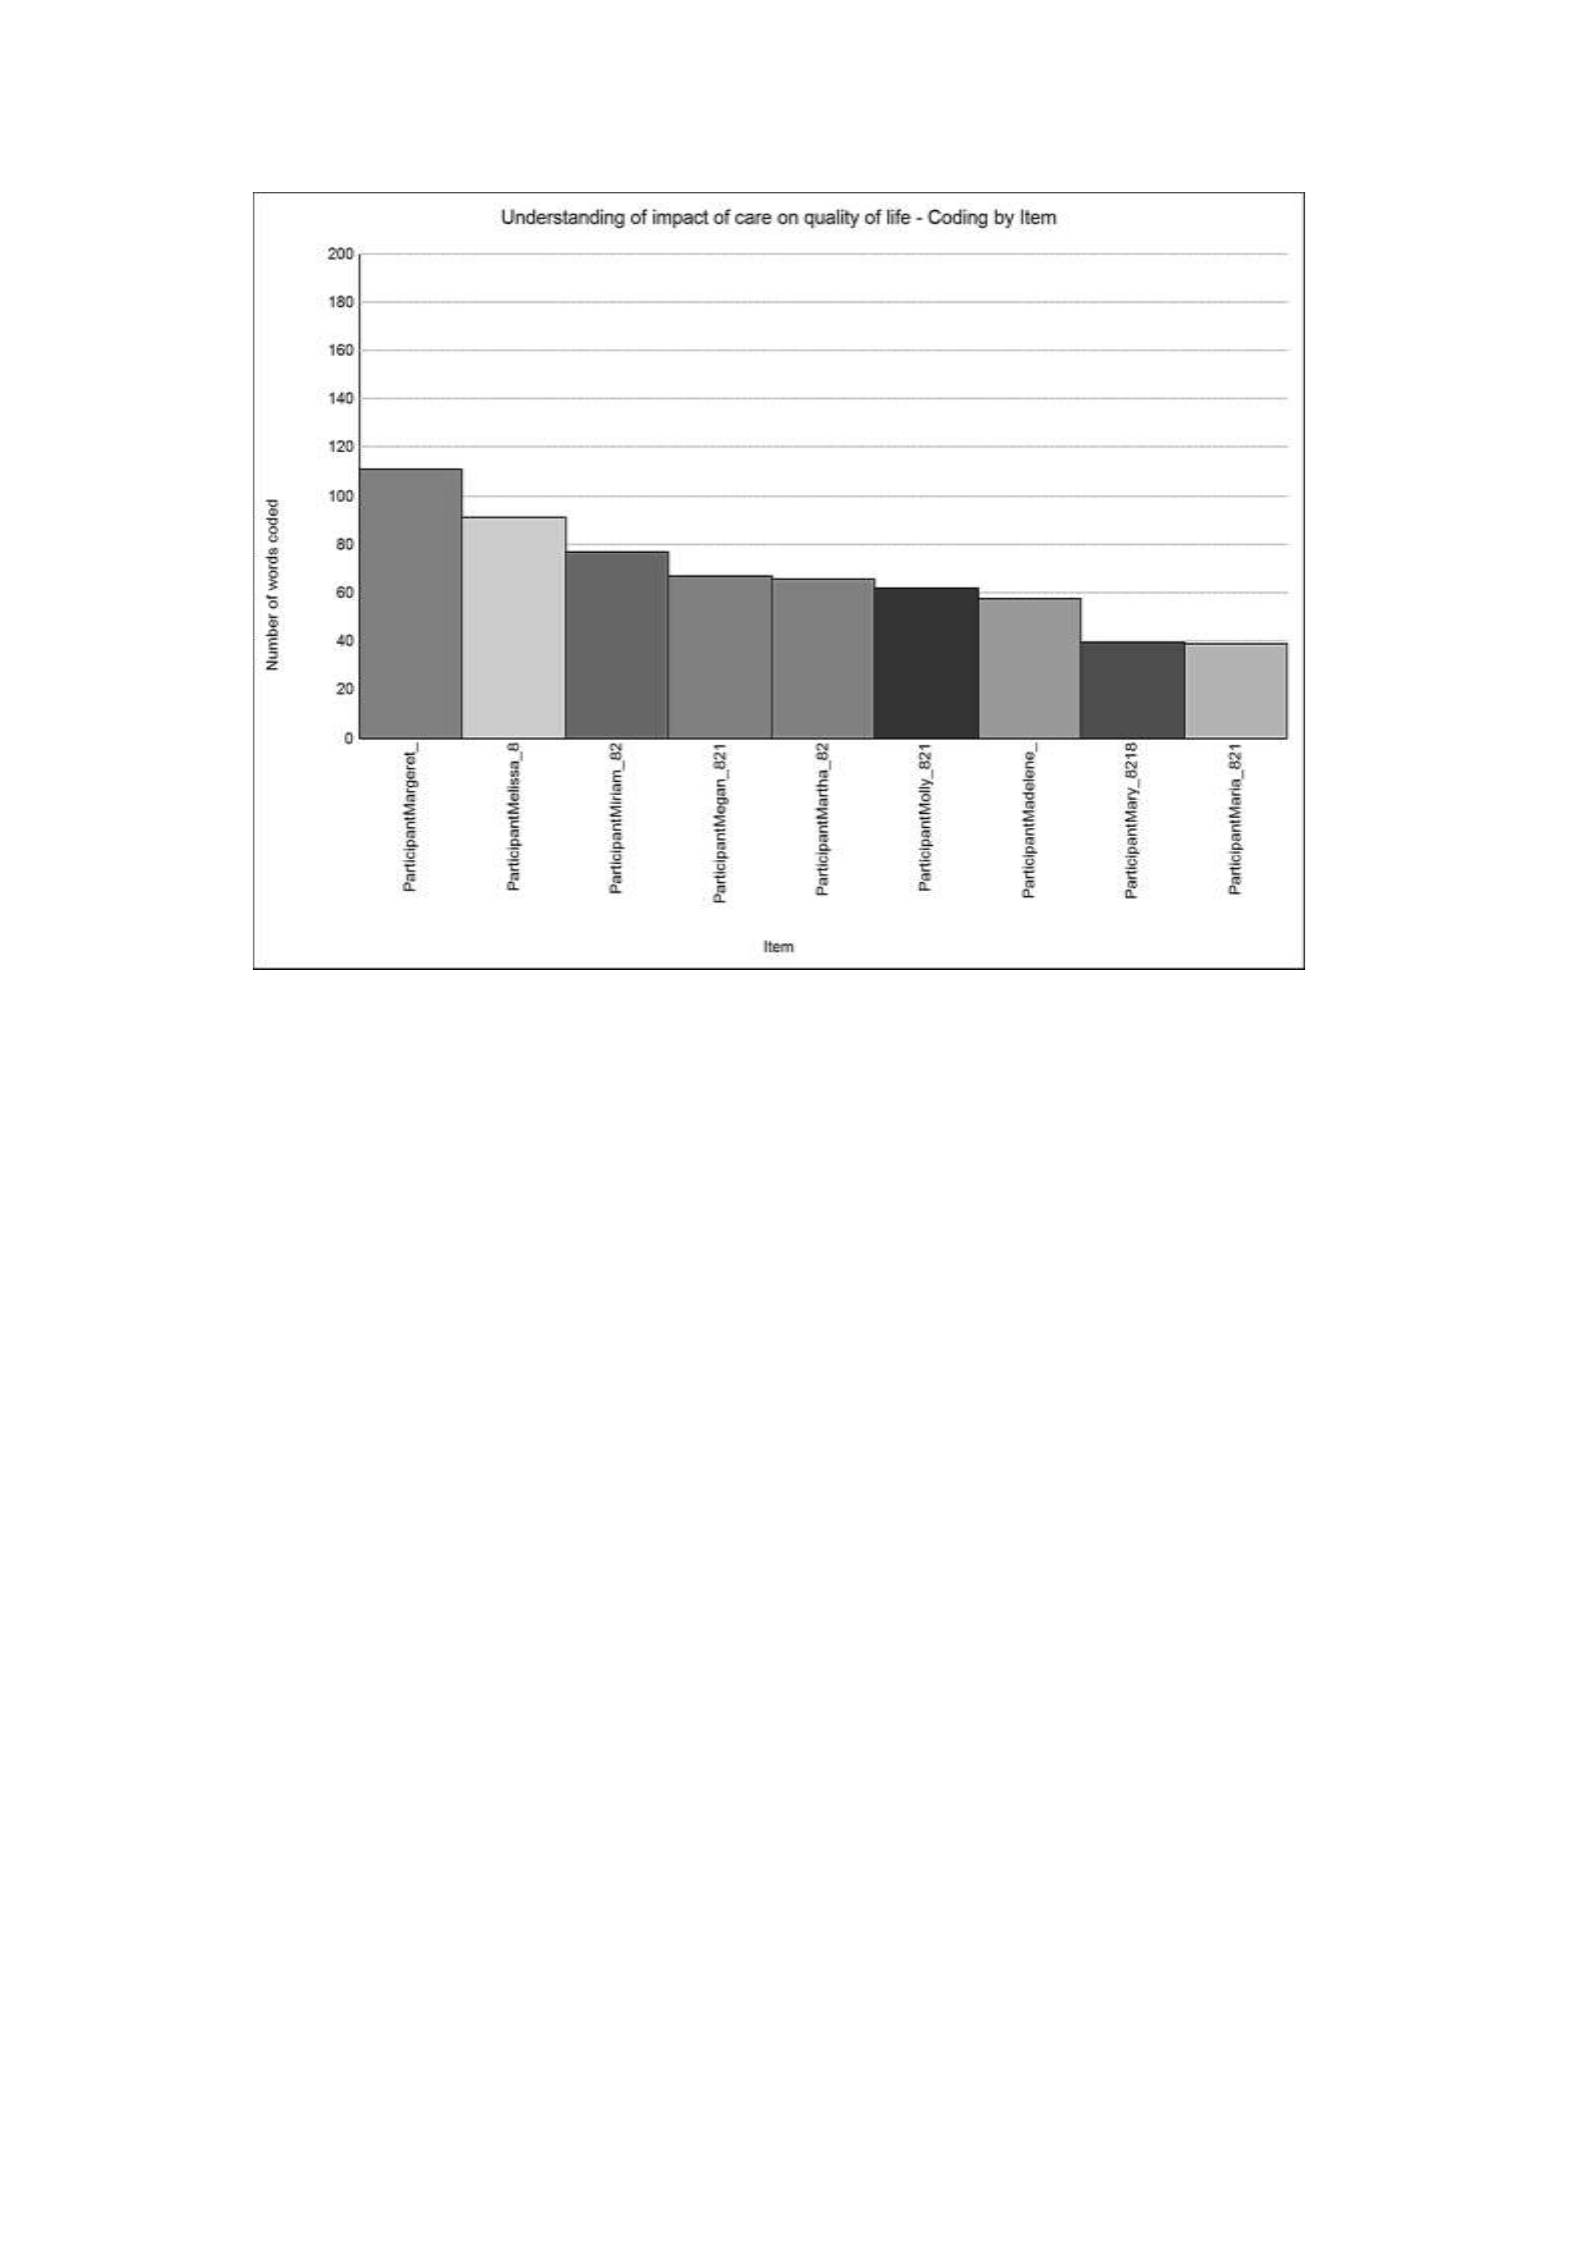
57
Figure 8. Understanding the impact of healthcare number of words coded per participant.
Summary
The interview with participants revealed that they understood access to healthcare, at least in terms
of
maternal and child care. They knew of the impacts of healthcare access on quality of life and knew
what they wanted from a healthcare provider. The participants perceived the healthcare they received
as poor and of substandard quality and highlighted ways that the healthcare failed to meet their needs
or expectations. They talked about the poor communication skills exhibited by their healthcare
providers including being rude, negligent and unprofessional, the unsanitary conditions of the hospital
and the shortage of supplies. In addition, they discussed the factors that made access to healthcare a
challenge. These factors include transportation and a shortage of healthcare providers. NViVo 11
qualitative analysis tool was used to analyze the responses of the participants. The emerging themes
were transport challenges, paying for healthcare, hostile hospital environment, timeliness of care and
patient experience with healthcare providers, patient safety, the impact of healthcare access on patient
outcomes and safety and impact of healthcare access on maternal and child mortality. The themes are

58
interpreted and discussed further in the following chapter. Chapter 5 will introduce a brief overview
of the seven themes identified in the previous chapter, an interpretation of findings, limitations of the
study, recommendations, implications for social change, and a conclusion.
Chapter 5: Discussion, Conclusion, and Recommendations
Introduction
The data analysis in Chapter 4 yielded six themes: transport challenges, paying for healthcare, hostile
hospital environment, timeliness of care and patient experience with healthcare providers, patient
safety, and the impact of healthcare access on patient outcomes and safety. These themes reflected
WCBAs’ perspectives about healthcare access in Cameroon, the quality of healthcare access, and their
understanding of the impact of healthcare access on quality of life. In this chapter, these findings are
interpreted and discussed by themselves and in the context of the literature. In addition,
recommendations are suggested, implications of the findings are discussed, and limitations of the study
are outlined.
Interpretation of Findings
The findings showed that transport challenges hindered access to healthcare due to several reasons
such

59
as lack of money and distance from the hospital. Some patients tried to walk in order to receive medical
care, but often, they were too weak. The consequences were delayed access to care when they arrived
too late to find out the doctor was gone for the day as well as postponement and missed appointments.
Some patients selfmedicated when they could not access the hospital, and others turned to traditional
medicine. For example, Martha had to endure pain despite being pregnant because she could not
afford to pay for transportation and waited until her scheduled antenatal visit to have a checkup. Others
like Melissa turned to options like pouring cold water on her child to reduce fever. All of these
consequences posed risks for mothers and children during pregnancy and the postpartum period.
Living in rural and/or remote areas further compounded the problem of poverty and difficulties in
accessing public healthcare services. The literature review highlighted some problems of healthcare
access for rural populations including distant health facilities, lack of means to reach hospitals, poor
knowledge of public health, and lack of funds to settle medical bills. The findings of this study
particularly acknowledge the long distance to hospitals and lack of money to pay for transportation to
reach hospitals.
Paying for healthcare is a major hurdle in terms of access to healthcare. Some patients had
public
insurance while others lacked insurance altogether. Out-of-pocket costs for healthcare were a major
challenge to all participants, since almost all identified as coming from low-income households. They
had to pay money to get transportation to the hospital, consult with doctors, and buy medications. The
participants were aware that they could not be treated if they did not not have money. For example,
Molly explained how one must have the full amount of money to get attended by a doctor, even in an
emergency situation. The situation is dire, according to Molly, because regardless of the patient’s
situation, treatment cannot be initiated unless the patient pays first. Ajong et al. (2016) reported a 25%
to 19% decrease in childbirth with medical practitioners between 1993 and 2003 as well as delayed
prenatal care in at least 45% of women. Although there are many factors that may be attributed to the
decrease in the number of practitioner-attended births, the costs of these services are an important

60
factor. The findings of the qualitative analysis also revealed that equity is a significant problem, as
money determined who gets access to healthcare services, including doctors and whose treatment gets
prioritized. In the literature review, factors that affected equitable healthcare access such as race,
ethnicity, religion, and gender were discussed, but social status and financial ability were not, because
often public health is meant to be accessible to all. However, among the participants, this was not
usually the case. Some participants were not insured and those who were received a public insurance
program. The Cameroonian government allocated only 6% of its budget on healthcare (Abrokwah et
al., 2016), and thus, it is possible that public health is significantly underfunded and patients have to
still pay for services out-of-pocket. In a country where 33% of the population lives below $1.25 a day
(World Bank, 2011), out-of-pocket payments for healthcare and mandatory payment before receiving
healthcare can be a significant hindrance to healthcare access.
From the data, it was also obvious that the hospital environment was not friendly to patients and
often
they had to endure just to get treatment. The patients complained of poor communication skills of
healthcare providers such as that nurses were rude, shouting at and humiliating participants in front of
other patients. The nurses were usually unprovoked, such as in the case of Mercy, who wanted to
notify the nurse about the pain she was having when the nurse humiliated her in the hospital lobby, as
well as Martha, who learned to cope with the nurses’ rudeness and shouting to get treatment, and Mary,
who had a book thrown at her for asking why her prescription was expensive. The participants also
highlighted unprofessionalism from healthcare providers who treated or prioritized some patients
based on their wealth or influence in the community. In a setting with limited doctors, patients who
had to see a doctor were likely to be affluent or influential in the community at the expense of clinically
serious cases. Patient care was unsatisfactory at times, and patients were forced to take care of
themselves. For example, Maria said she would get water for the shower by herself because the nurse
said she did not have the time to do so. Miriam explained how one had to be vigilant to ensure they
get the right treatment. Mary explained how she went without food while being admitted. These

61
findings were consistent with those discussed in the literature review who reported scolding of women,
verbal abuse, negative personnel attitudes, and slapping of women during labor and delivery.
Considering the nursepatient ratio of 1.6 nurses for 1000 people (World Bank, 2011) and even more
serious discrepancies of nursepatient ratios in rural areas (CDBPH, 2012), it may be that nurses are
overworked and amidst all other challenges of the Cameroonian healthcare system, they have to do an
almost impossible task. Overworking may also result in burnout syndrome, particularly where the
nurses are not adequately supported and their mental health is not prioritized within employment
contexts. Occupational stress has an impact on nurses’ caring behaviors (Sarafis et al., 2016).
All participants perceived the quality of care they received as being low. Using three patient care
metrics, timeliness of care, patient experience, and patient safety, the findings revealed that the quality
of care is not satisfactory. First, healthcare was not timely. Patients had to wait long times to get access
to healthcare providers. Patients also had to wait for long times at the lobby despite their condition.
Meghan said that, she had to wait for a long period despite the fact that she was in pain and no nurse
seemed to bother. Triage sorts out patients according to urgency or emergency, resulting in better
patient flow, reduced wait time, and better patient satisfaction (Jarvis, 2016). However, it is not clear
the extent to which such and other measures are taken to improve the overall patient experience and
hospital efficiency in the setting where the study was conducted.
The long wait times are sometimes caused by many patients and inadequate human resources. The
patients often have to consult with nurses, who are also involved in treatment and prescribing because
doctors are unavailable or inaccessible. Where doctors are available, they may be too few to see all
patients, and when they do, they do not have adequate time and hence conduct a short patient
assessment as some patients said that the doctors only spend a few minutes with them. The literature
review highlighted some of these challenges with healthcare providers particularly the shortage of
doctors and nurses. The doctor to patient ratio in Cameroon is two doctors per 10,000 people, well
below the recommended minimum of 23 for every 10,000 people (Poverty and Health, 2013). Rural

62
areas such as the setting of the present study are likely to have even fewer doctors. With fewer
healthcare providers, the queues and wait times are long, and the few available doctors cannot attend
to all patients. When they attend to patients, they are allowed a few minutes for each, such that the
patient feels like they did not get adequate time with the doctor. The length of time a doctor spends
with the patient is often used by patients to judge the satisfaction they can attach to their healthcare
service (Surbakti & Sari, 2018). A short patient-doctor experience may contribute to patient
dissatisfaction with their care. When the patient’s condition is out of scope for the nurse, the patient
has to wait until the doctor is available despite their health condition or emergency. For example,
Meghan explained how she had to wait in the lobby for a doctor because the nurse did not know what
to do.
The findings also point to shortages of medical supplies and an unsanitary hospital
environment
which put patient safety at risk. All participants acknowledged that the hospital they visited lacked
adequate medical supplies. In some instances, patients were asked to purchase these supplies before
they could receive treatment. Such supplies include syringes, wound dressings and bandages. This is
an additional financial burden to patients who are barely able to pay for healthcare. In addition, there
is a patient safety risk in case some supplies such as syringes are used on multiple patients as Mary
said that she had observed this happen. Besides the shortage of supplies, the participants described the
hospital as being unsanitary, smelly and dirty. In other cases, there were problems with lighting and
patients had to stay in the dark. All of these factors can compromise patient safety and thus, influence
the quality of care that patients receive. Shortage of medical supplies can be directly attributed to
healthcare funding challenges. In the literature review, insufficient government expenditure was
explained as the root cause for a shortage of essential materials such as equipment, beds, and drugs.
The 27% healthcare burden that the government finances (World Bank, 2013) may not be adequate
even when patients have to pay.

63
The findings revealed that the participants understood the impact of healthcare services on their
lives. They talked about how poor healthcare could lead to death or adverse effects. Thus, two themes
were created; impact on patient outcomes and safety and impact on maternal and child mortality. On
the impact of patient outcomes and safety, some participants noted that the quality of healthcare they
received impacted their healing process. Melissa said that the negligence that nurses exhibited might
impact the healing process. The nurses also prescribed medicine which according to her did not work
and had to endure pain for several days before she got new medication. Nurses’ roles are not to
prescribe medication, and there are consequences when healthcare providers do not play their roles as
should be. Long wait times at the hospital also impacted patient outcomes and safety for Margaret
whose child convulsed when she stayed too long at the hospital lobby without attention. Triage is
supposed to deal with some of these issues by prioritizing patient care according to urgency. However,
this does not seem to occur and patients’ outcomes, safety, and lives are at risk.
The participants also understood that healthcare access had an impact on maternal and child
mortality. Most participants feared that the negligence at the hospital was a threat to all their lives. For
example, Maria talks of how she as bleeding and the nurse were not concerned for at least several
hours. She said she was scared she was going to die. Martha also acknowledges how the lack of basic
healthcare can lead to worsening of sicknesses leading to death. Mary said that the sharing of syringes
that she observed in addition to the unsanitary conditions in the hospital could cause maternal or child
mortality. Meghan recalls when a pregnant mother died because she could not afford money for a C-
section. All of these instances show that these participants are well aware of the impact that healthcare
access has on their health and life.
The above findings are in agreement with those reported in previous research. Women, especially
from
low-income households, still have to use public health services regardless of their perceptions due to
lack of alternatives. These sentiments are shared by Fotso and Mukiira (2011). Consistent with Odetola
(2015), economic and health-system factors such as quality of care, scarcity of healthcare facilities

64
and personnel and demographic variables like educational level and income influence patients’
perceptions. However, it is not completely accurate what Soh (2013) said that the WCBA in Cameroon
fail to access healthcare because they do not recognize it as a fundamental health right. They perceive
healthcare access as important for themselves and their children and whatever factors that delay
healthcare access are often beyond their control. Factors such as finances, transport challenges, a
hostile hospital environment where healthcare providers are often rude and unprofessional, long wait
times and unavailability of healthcare personnel, shortage of supplies and unsanitary hospital space
all contribute to the extent that WCBA access healthcare and the quality of healthcare they can get.
Thus, the problem of healthcare access is more systemic and institutional than it is patient-focused.
Also, religious and sociocultural practices did not influence healthcare access as reported by CDBPH
(2011). At the end of the day, all the women interviewed wanted quality healthcare despite their
sociocultural or religious
beliefs.
Theoretical Lens
The utilization model developed by Adey and Anderson in the 1960s was utilized to facilitate
understanding of access to healthcare. The examination of the lived experiences of WCBA using the
healthcareutilization model provided a clearer view of women’s access to healthcare in Cameroon.
This model helped facilitate a comprehensive understanding of the reasons for poor access of
Cameroon women to healthcare services.
Study findings revealed the existence of several impediments in the process of access to healthcare
by
the study population. These were attributed by a number of factors to include; inadequate healthcare
provider team (doctors and nurses), transportation challenges, inadequate healthcare financing, and
shortage of medical equipment and supplies. The findings also showed that WCBA in seeking access
to healthcare not only encountered these challenges but were aware of the effects of healthcare on their
outcomes and safety as well as maternal and child mortality. The conceptualization of the healthcare

65
utilization model covered all aspects of this study. There are systemic challenges that affected
healthcare access and these need to be adequately addressed to reduce maternal and child mortality
among women of child-bearing age.
Limitations of Study
The sample size (10 participants) may have been too small or homogeneous to make accurate
generalizations. For example, the literature review showed that religious beliefs, sociocultural values,
and perceptions of WCBA might influence access to healthcare. However, this was not the case with
the study participants, which may be because the sample was not heterogeneous enough. Time,
resources and personal bias were also a major limitation. The process of analyzing and making sense
of the data was a time-consuming exercise. My prior knowledge of the health care challenges of this
population (WCBA) presented some degree of bias. This was minimize using a reflexivity strategy to
ensure my preexisting knowledge of the study did not influence the research process.
Recommendations
Regular training of nurses and doctors can equip them with communication skills to enable
them to communicate with patients more effectively. Motivation and discipline by the hospital
management can also help inspire accountability and can contribute to better patient care. The second
set of recommendations are systemic and aim to address systemic issues that plague the healthcare
system in Cameroon and which have a direct impact on maternal and child care. Higher budgetary
allocations and more collaborations between the private and public sector as well as the donor
community can help increase funding and boost healthcare resources. In addition, I recommend the
utilization of community nursing programs where healthcare practitioners travel to communities at
least to conduct check-ups and alleviate the need for patients to travel long distances to get to hospitals.
In addition, incorporating traditional medicine into healthcare particularly in rural areas can help. This
would be done through training traditional birth attendants to conduct uncomplicated births in rural
areas. A systematic review by Byrne and Morgan (2011) showed that traditional birth attendants could

66
be integrated with formal health systems successfully to increase skilled birth attendants. The WHO
(2015) suggested the incorporation of traditional birth attendants into formal healthcare after further
research.
Traditional medicine has been explored as a complement to western medicine style, and certain aspects
of traditional medicine can be investigated further for use by women in rural areas and who cannot get
to hospitals in time. The participants in the study already admitted to using traditional medicine when
they could not access healthcare. Further research is required to assess how traditional medicine can
be incorporated into current practice. Lastly, motorcycles common in many rural areas in African
including Cameroon can be modified to provide “ambulatory” transport to hospitals during
emergencies particularly in areas with limited access. They have been implemented in villages in
certain areas in Uganda, Kenya and Malawi. Hofman, Dzimadzi, Lungu, and Ratsma (2008) reported
that motorcycle ambulances in Malawi were useful and affordable means of referral for emergency
obstetric care.
Implications for Social Change
The present study has shown that women know and understand the importance and impact of
healthcare access not only on the quality of life but also on the lives, health, and safety of themselves
and their children. They have borne the pain of an underfunded healthcare system with significant
challenges such as shortage of supplies, unsanitary conditions, poor attitudes from healthcare
practitioners and a shortage of healthcare providers. Most of the time they cannot afford to pay for
healthcare services, transport and even when they do, they are frustrated that they still cannot get to
consult with a doctor and sometimes are not treated so nicely.
The study has shown that there is a big problem with healthcare facilities as well as systematic
problems
with the healthcare system. All is not lost because there is so much that can be done to help these
women and children particularly those living in rural and/or remote areas. Adopting practices,

67
infrastructure, and mechanisms that are adaptable to these regions as suggested above can help address
some of these challenges.
For social change, the findings of the present study show that the biggest problem is not with the
patients (women of child-bearing age), but with the healthcare system. Thus, attempts to improve
maternal and child care, can be solely targeted at making public health more accessible and
accommodating to these women and not changing their perceptions.
Conclusion
The purpose of this qualitative study was to examine how WCBAs seeking healthcare services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. The study aimed to answer three research questions. The first research question was: how
do WCBA seeking maternal/child healthcare services in Cameroon perceive the process of healthcare
access through health institutions? The findings of the study showed that WCBA perceived the process
of seeking maternal/child healthcare as a difficult one characterized by challenges in getting transport
to medical facilities because they cannot afford it or live too far from the hospital, challenges in paying
for healthcare because they pay out-ofpocket, come from low-income households and most are
unemployed or employed only part-time and without much social support. They also have to withstand
a hostile hospital environment as characterized by poor communication skills and unprofessionalism
of the nurses. The patients often had to endure insults, negligence, and humiliation from the healthcare
providers and do not always get access to doctors. However, they persevere for lack of alternatives.
The second research question was: how do WCBA seeking maternal/child healthcare services
in Cameroon perceive the quality of healthcare services offered through healthcare institutions? The
study found out that WCBA seeking maternal/child care have to deal with shortages of medical
supplies and healthcare providers and unsanitary conditions, which influence timeliness of care,

68
patient experience, and patient safety negatively. Thus, the participants perceived the healthcare they
receive as being of poor quality but still have to use it because private care is out of their reach.
The third question was: how do WCBA seeking maternal/child healthcare services in Cameroon
understand the impact of healthcare services on their quality of life? The study found out that WCBA
seeking maternal/child healthcare services understood the impact of healthcare services on the quality
of life. They were aware of the effects of healthcare on their outcomes and safety as well as maternal
and child mortality. Some had observed and experienced maternal, and child mortality due to
negligence at the hospital and they are constantly afraid that they are not safe. In conclusion, there are
systemic challenges that affected healthcare access and these need to be adequately addressed to
reduce maternal and child mortality among women of child-bearing age.
For over 30 years, access to healthcare by Cameroon’s women of childbearing age (WCBAs) has
remained a significant health challenge. WCBAs in a majority of countries in the global south,
including some developed countries, are facing challenges related to healthcare access, even in the
presence of well-developed infrastructures, technologies, and economies (Imo, Isiugo-Abanihe, &
Chikezie, 2016). Reasons for these challenges include that the majority of medical innovations,
developments, and information are only discussed theoretically rather than being fully and practically
incorporated into the healthcare sector. Cameroon, located in central Africa, with an estimated
population of 21.7 million inhabitants, is facing the same challenges related to healthcare access (Koh
& Nowinsky, 2010).
Maternal and fertility health continues to be a major public health concern among WCBAs
(World Health Organization [WHO], 2012). The WHO indicated that, each year, about 8 million
women suffer from pregnancy-related complications, and over 500,000 maternal deaths occur, many
of which could have been prevented with adequate healthcare (Abrokwah, Moser, & Norton, 2016).
This situation is also occurring in the rural communities of Cameroon. This chapter contains relevant

69
background information, current health problems in Cameroon, social determinants of health in
Cameroon, problem and purpose of the study, research questions, and a conceptual framework to guide
the design and address the research questions. This chapter also defined key terms used in this study.
Background of the Study
Women’s health should be taken seriously by every nation’s political and health leadership.
Comprehensive care promotes good health for women and their families throughout their lives, from
prevention of premature delivery and low birth weight to childhood nutrition and immunization and
prevention and treatment of chronic conditions such as heart and lung disease, mental health disorders,
diabetes, and cancers
(Quick et al., 2014). Like many other countries, Cameroon’s WCBAs have struggled with poverty,
unemployment, lack of sufficient social services, and minimal investment in social amenities
(Tchombe et al., 2012; Ukpere, 2011).
Cameroon’s women who have reached the age of childbearing are some of the most adversely
affected demographic populations (Chandra-Mouli, Camacho, & Michaud, 2013). Poverty and lack of
healthcare has mainly affected women living in rural areas who have difficulty accessing public health
services due to a number of challenges: (a) distant health facilities, (b) lack of funds to settle medical
bills, (c) poor knowledge of public health, and (d) lack of means to reach hospitals (Egbe, 2014). For
these reasons, many women often depend on medical aid such as maternal and child healthcare
services from health service providers, primarily religious organizations and non-governmental
organizations (NGO) personnel who travel to villages (Soh, 2013).
The health of WCBAs in the southwest region of Cameroon is of great concern and limited
data exists regarding how women in these regions perceive their health and healthcare access (Deaton
& Tortora, 2015). WCBAs in Cameroon, particularly in poor rural communities, have limited access
to healthcare facilities and services that cater to their healthcare needs (Weinger & Akuri, 2007).
WCBA do not consider healthcare to be their fundamental human right (Soh, 2013).

70
To improve modern healthcare awareness and minimize gender inequality in healthcare provision,
Cameroon is interested in changing perceptions and access to healthcare among WCBAs (McTavish
& Moore, 2015; Soh, 2013). Efforts to improve healthcare access in the southwest region of Cameroon
have received support from independent organizations such as the Cameroon Healthcare Access
Program and the WHO (Abrokwah et al. 2016). To effectively evaluate the healthcare access problem,
it is important to also understand related challenges to improve the level of health services in the
country. These challenges have led to low levels of acknowledgment of modern health services and
reduced access to services among WCBAs. In light of these challenges, this study focuses on
understanding perceptions about access to healthcare among WCBAs in the southwest region of
Cameroon.
Current Health Problems in Cameroon
Stakeholders widely recognize that factors contributing to high maternal mortality include the
low quality of service during delivery and the lack of healthcare facility access for WCBAs in
Cameroon (Egbe, 2014). For example, from 1993 to 2003, childbirth with medical practitioners
increased from 85 to 90% for the richest quintile, but fell from 25 to 19% for the poorest (Ajong,
Njotang, Kenfack, Yakum, & Mbu, 2016). Also, 45% of pregnant women wait until the second or third
trimester to seek prenatal care, when it is often too late to adequately anticipate complications (Ajong
et al., 2016).
In general, access to medical services for many WCBAs in developing countries is low (Soh, 2013).
The
extreme shortage of primary care doctors, lack of infrastructure, corruption, low per capita health
expenditure, and economic growth aggravate problems with access to care (Business Monitor
International, 2014; Poverty and Health, 2013; World Justice Project, 2013). Cameroon has one of the
most notorious reputations in Africa in terms of poor maternal healthcare. The country has made global
headlines a number of times involving health indicators of countries in the global south, due to the
deaths of pregnant women who were unable to access healthcare services (Business Monitor

71
International, 2014; Poverty and Health, 2013; WHO, 2012; World Justice Project, 2013). The
country’s Ministry of Public Health indicated that 9,000 women died during childbirth in 2010 (Leina,
2011). Further, the government “attributes its maternal mortality problem to the absence of adequate
maternal care” (Leina, 2011, p. 1). Some reasons women prefer not to seek healthcare services include
the lack of societal permission to do so, poverty, distance to health facilities, and fear of going alone
(Ibrahim et al., 2013). Therefore, a need persists to understand WCBA perceptions regarding their
access to healthcare, which is clearly affected by the current healthcare system and related
mechanisms.
Nurses are the primary providers of healthcare services and in Cameroon, the nursing profession is
facing funding shortages because the government has dedicated only 6% of expenditures to healthcare
(Ajong et al., 2016). A majority of healthcare facilities in Cameroon are charging high prices, and as
a result, poor families are turning to traditional healers and self-healing methods (Ajong et al., 2016).
In addition, poor water quality and sanitation is causing women’s poor health (Kruk, Porignon,
Rockers, & Van Lerberghe, 2010). Only 40% of the population is receiving pipe borne water (Ajong
et al., 2016). The remaining population lives in areas using improper sanitation practices. All of these
issues contribute to a decreasing life expectancy of the population by 2 years (Kruk et al., 2010).
This study could help the Cameroon legislature consider the healthcare system and its effects
on WCBAs. As a result of this study, the healthcare success of Cameroon women may increase through
the creation of new laws. This study may also serve as a guide to healthcare advocates who are working
to improve the health status of Cameroon. These efforts can bring dramatic changes to the healthcare
system of Cameroon.
Problem Statement
WCBA in Cameroon, particularly those in poor rural communities, have limited access to healthcare
facilities and services that cater to their healthcare needs (World Bank, 2013). Although a vast majority
of these women have concerns about their health and recognize a variety of factors that endanger their

72
health, they have previously had little information regarding how to seek healthcare services. Instead,
they place the burden of maintaining their health on themselves (Weinger & Akuri, 2007). Therefore,
most WCBAs will not perceive government healthcare services as an option in maintaining their
health. Mismanaged healthcare facilities as well as women’s sociocultural status in terms of healthcare
access and financial vulnerability impact this population negatively (Soh, 2013).
Despite a growing need for a sustainable and affordable healthcare system that meets the basic
healthcare needs of WCBAs who need medical care, a gap persists in understanding the reasons
involving inaccessibility issues and how such issues have influenced the personal satisfaction and
health awareness frameworks that do exist. Literature from government reports in this area are limited,
and directing an investigation into healthcare access for WCBAs could reveal essential factors
regarding how this populace sees current medical services in Cameroon and their view of what
potential outcomes exist for making change.
Purpose of the Study
The purpose of this qualitative study was to examine how WCBAs seeking healthcare services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. Also, this study discerns how WCBAs perceive access to healthcare institutions.
Examining how WCBAs in Cameroon perceive the quality of the healthcare services offered and how
this impacts their quality of life is significant. A study of this nature may provide data useful in
recommending solutions to the problems involving shortages of healthcare professionals,
infrastructure, economic conditions, financial discrepancies, access to technology, and management
of the system.
Research Questions
I formulated three phenomenological study questions, which I used to obtain the responses
needed to understand the perception of access to healthcare by WCBA in rural communities in Mamfe
Cameroon.

73
RQ1: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the process
of
healthcare access through health institutions?
RQ2: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the quality
of
healthcare services offered through healthcare institutions?
RQ3: How do WCBAs seeking maternal/child healthcare services in Cameroon understand the
impact
of healthcare services on their quality of life?
Theoretical Framework
The conceptual framework for this qualitative study was Andersen’s healthcare utilization
model. Andersen & Newman (2005); Rigg, Cook, & Murphy (2014), viewed the idea of access in a
variety of ways. According to Andersen & Newman (2005), the characteristics of a population as the
major factor in designing the access framework. Rigg et al. (2014) believe that health outcomes should
be the main determinants of a healthcare access model Despite ongoing debates regarding the concept
of access, the healthcare sector accepted the notion that the reach of urban and rural healthcare
facilities, medical personnel, and quality of healthcare service differs markedly.
According to Aday and Anderson (1974), financial ability is a significant indicator of the level
of access to quality healthcare, which further defines the boundary of access to healthcare between
urban and rural populations. Use of the healthcare utilization model allowed me to address (a) how the
process of healthcare access is perceived by WCBAs in Cameroon, (b) how the quality of healthcare
is perceived by WCBAs in Cameroon (c) how WCBAs understand the impact of healthcare services
on their quality of life. This conceptual model recognizes access as involving the relationship between
characteristics of the healthcare service system and potential users in a specified area, moderated by
healthcare public policy and planning efforts (Pemunta & Fubah, 2015).
The knowledge obtained through qualitative methods illuminated the intersectionality of problems
such

74
as poverty and suffering, and people’s inability to access appropriate healthcare, thereby providing the
basis for planning and implementing equitable care at local and national levels. Contextualized
knowledge also helps one appreciate the strength and agency that individuals possess in relation to
their health and healthcare. An examination of the lived experiences of WCBAs using the healthcare
utilization model provided a more nuanced view of women’s access to healthcare in Cameroon
(Levesque et al. 2013). This perspective was useful because this multilayered analysis gives insight
into how class and gender identities, among others, determine the social and material conditions of
women’s lives and makes explicit how complex interdependencies organize WCBA experiences. This
model was helpful in attaining a comprehensive understanding of the reasons for poor access of
Cameroonian women to healthcare services. This framework was also helpful in analyzing the
perspectives of Cameroonian women about the quality and impact of healthcare services.
Andersen’s conceptual framework also focuses on the individual as the unit of analysis and
goes beyond healthcare use, adopting health outcomes as the endpoint of interest (Pemunta & Fubah,
2015). The framework added genetic susceptibility as a predisposing determinant and quality of life
as an outcome (Pemunta & Fubah,
2015). By using the framework’s relationships, one can determine the directionality of the effect
following a change in an individual’s characteristics or environment. For example, if one experiences
an increase in need as a result of an infection, the Andersen model predicts this will lead to increased
use of services. One potential change for a future iteration of this model is to add genetic information
under predisposing characteristics. As genetic information becomes more readily available, it seems
likely this could impact health services usage, as well as health outcomes of study population (Pemunta
& Fubah, 2015).
Through this model, one can comprehensively examine the reasoning behind decreased accessibility
to
healthcare services. This model allows participants to openly share their opinions about current
healthcare status in Cameroon.
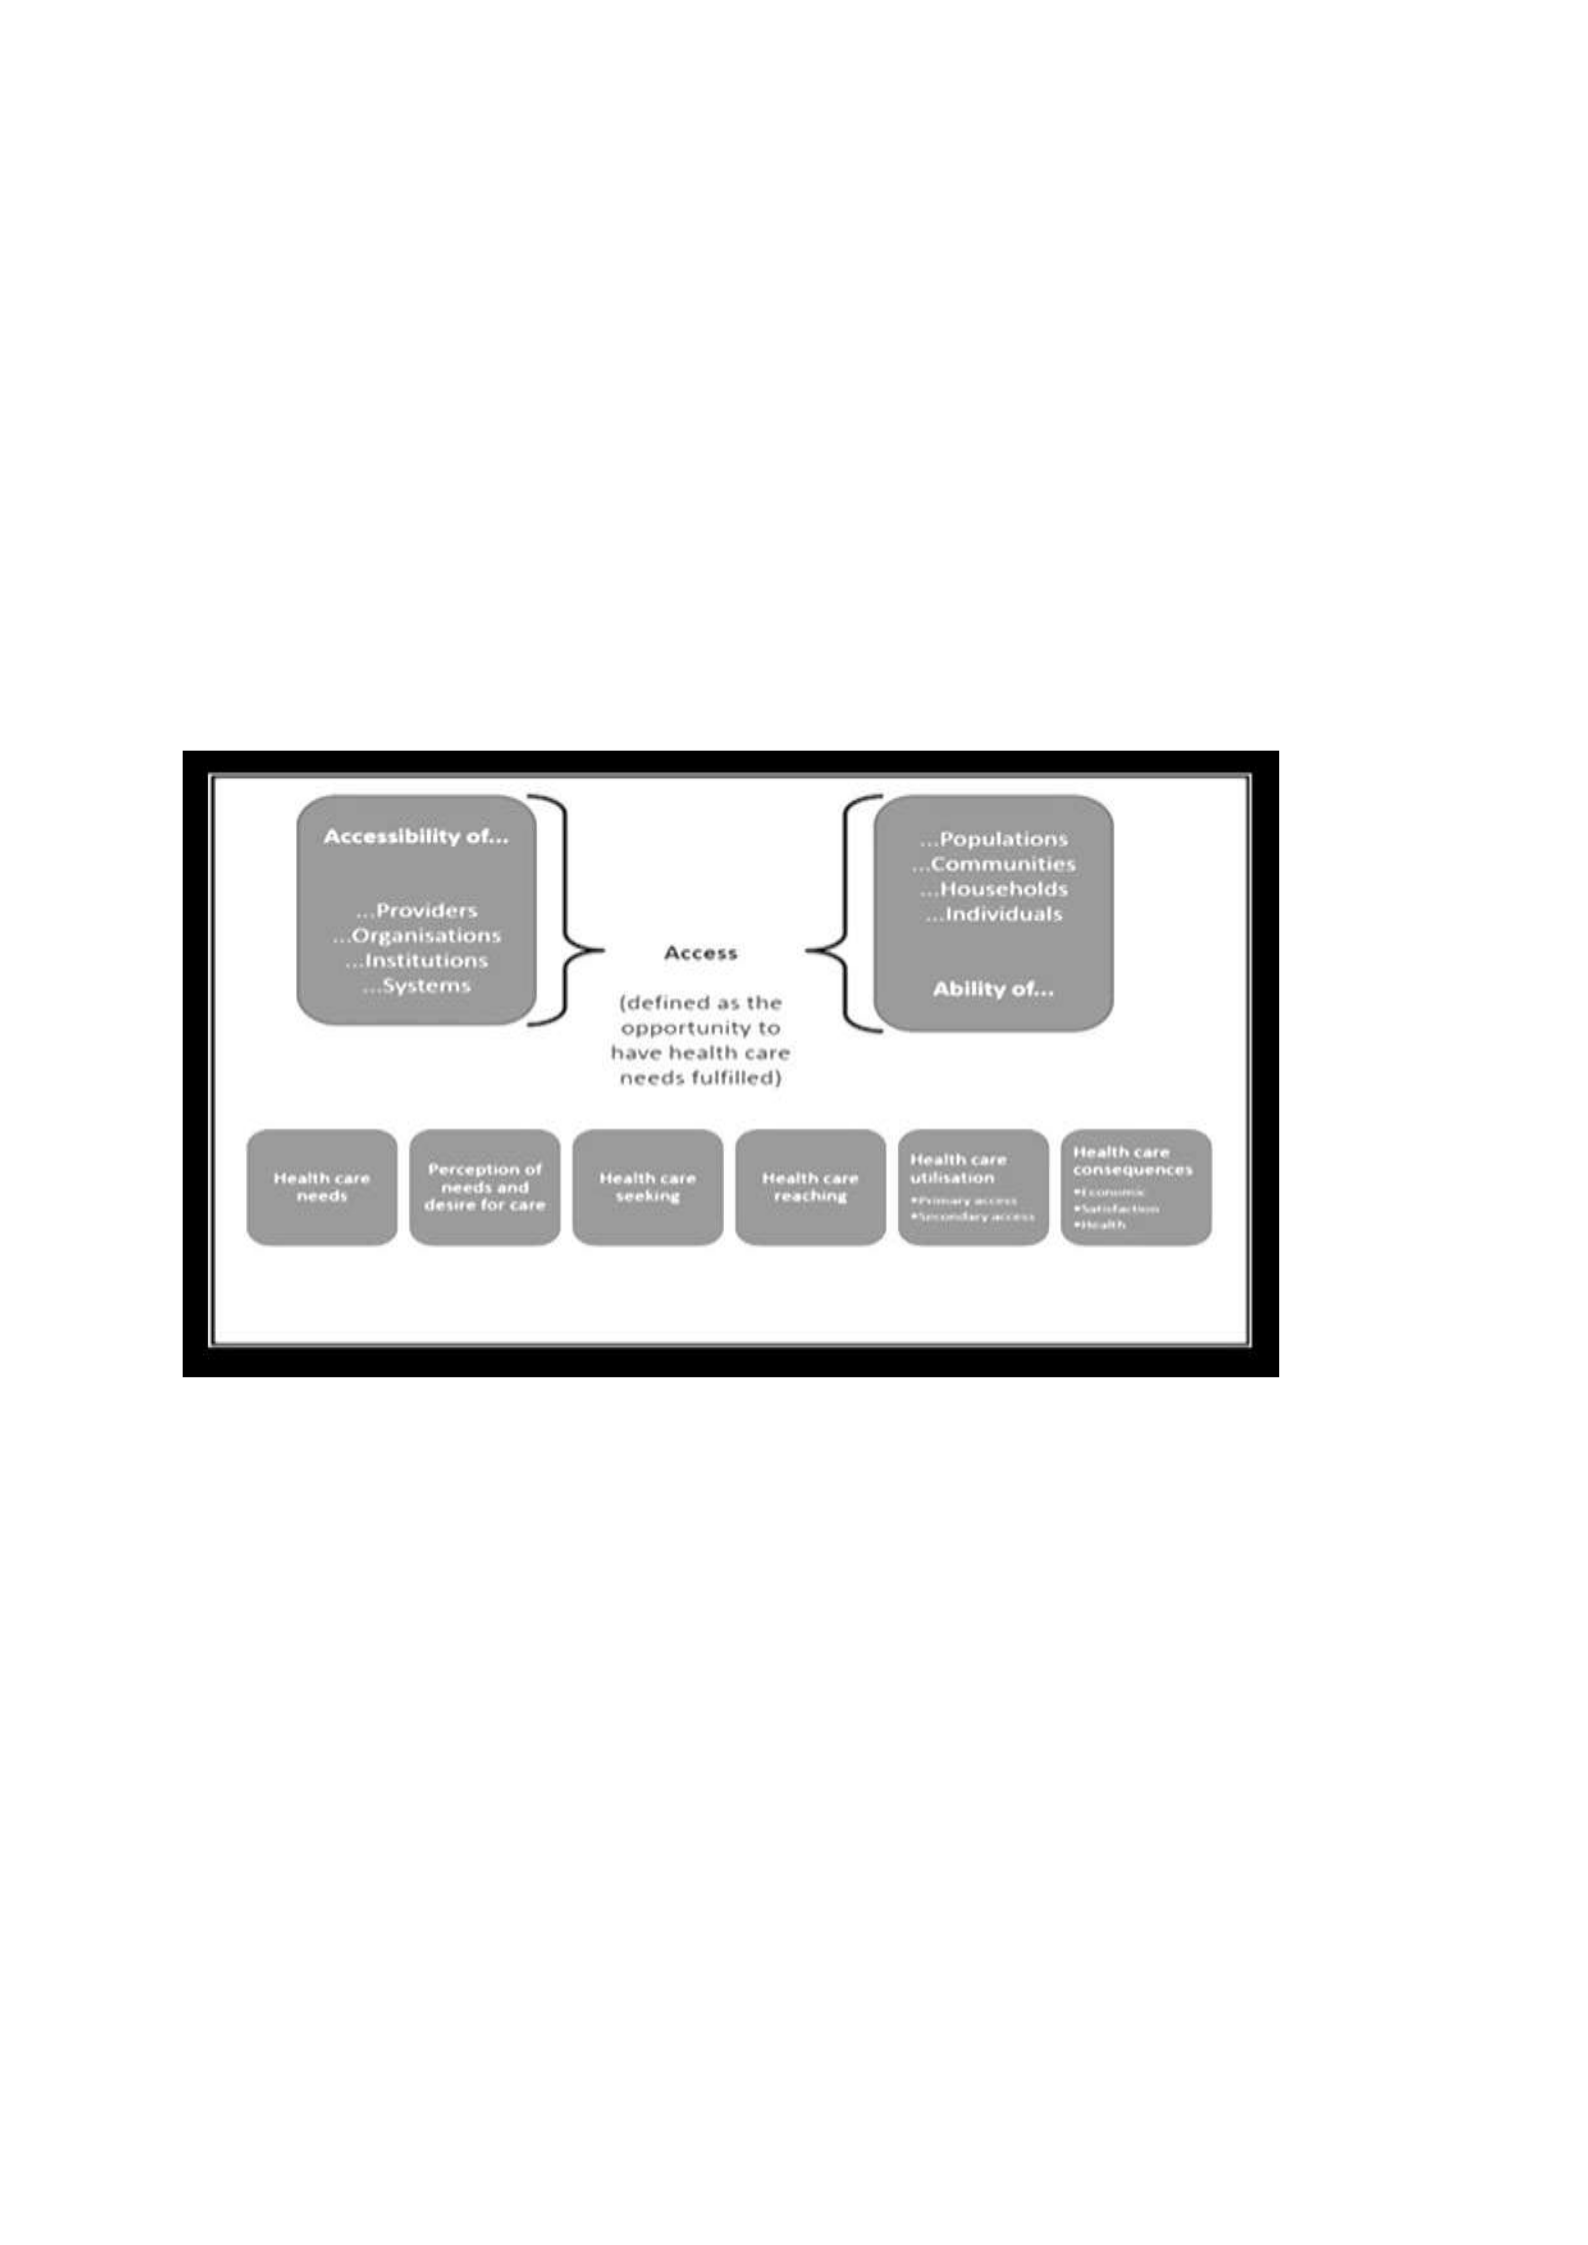
75
The health and medical field conventionally used the health belief model and Andersen’s
theoretical models to explain services use. The Andersen model, which explains that predisposing,
enabling, and need factors determine services use, is used broadly as a theoretical model that analyzes
predictors of health services use. The healthcare utilization model will be suitable when exploratory
research is needed due to lack of previous studies regarding perceptions of women about healthcare
services in Cameroon.
Figure 1. A graphical illustration of the healthcare utilization model. Note. Adapted with permission
from “Employment of Andersen’s description of the healthcare utilization model” by Levesque et al.
(2013), International Journal for Equity in Health, 12(1), 18.
Nature of the Study
This study used a qualitative phenomenological approach. The phenomenological methodology
allows
patients to express their issues related to healthcare services and ideologies related to quality health
(Rudestam & Newton, 2015). This methodology also permits patients to express their ideas about how
they give meaning to life events and how they perceive those events (Rudestam & Newton, 2015).
I explored perceptions regarding healthcare access or crises for Cameroonian WCBAs. Contextual

76
knowledge from target populations and key institutional actors in this rural setting in Cameroon could
inform the management regarding healthcare access challenges, health policy, and practice. This study
could inform the Cameroonian government and healthcare system of issues involving equity and
vulnerable populations during the development of strategies to increase interventions and reach
national health goals.
I used semistructured face-to-face interviews. Participants were encouraged to narrate their
personal experiences freely. Participants were WCBAs in Cameroon ranging in age from 18 to 45
years who could understand and speak English. It was necessary that participants speak and understand
English to facilitate communication and collect accurate data. I used a purposive sampling technique
and employed Colaizzi’s seven-step descriptive phenomenological strategy to describe and analyze
collected data.
Operational Definitions
Health Disparity: The differences adversely affecting socially disadvantaged groups which may
reflect
social disadvantage, but causality need not be established (Braveman et al., 2011). This definition is
grounded in ethical and human rights principles and focuses on the subset of health differences
reflecting social injustice, distinguishing health disparities from other health differences. According to
the National Institutes of Health (2015), it is the differences in the incidence, prevalence, mortality,
and burden of diseases and other adverse health conditions that exist among specific population
groups.
Global south: Developing or low- and middle-income countries. The term global south is also used
because of its significance from the postcolonial feminist perspective.
Healthcare access: Ability of a population to reach healthcare providers without financial,
organizational, social, or cultural barriers, and use services to preserve or improve their health
(Gulliford et al., 2012).

77
Health equity: The principle underlying a commitment to reduce and ultimately eliminate disparities
in
health and its determinants. Pursuing health equity means striving for the highest possible standard of
health for all people and giving special attention to the needs of those at greater risk of poor health
based on social conditions (Braveman, 2014).
Maternal/child health: Maternal health is the health of women during pregnancy, childbirth, and the
postpartum period, while child health is a state of physical, mental, intellectual, social and emotional
wellbeing and not merely the absence of disease or infirmity (WHO, 2012). Many factors affect
pregnancy and childbirth outcomes, including preconception health status, age of the mother, poverty,
and access to appropriate healthcare during and after pregnancy (Healthy People 2020, 2015).
Assumptions
The study assumed participants voluntarily shared their lived experiences pertaining to the
phenomenon of healthcare access in Cameroon by being truthful in their answers to all interview
questions. I assumed participants spoke English and understood questions during the interview
process. I also assumed that readily available literature on the phenomenon under investigation will
help inform development and implementation of effective policy and program interventions to address
the fundamental causes of healthcare access challenges for this population.
I assumed that creating awareness among this population will increase demand for healthcare,
improved knowledge will change health behavior, and women will access health services such as
prenatal care and have facility-based deliveries if services are available. To avoid the effects of
assumptions on the study, I performed purposive sampling. Through purposive sampling, the creation
of bias was prevented at every stage of the study. The use of purposive sampling targeted the
population under study and helped to reach the targeted sample more quickly.
Scope and Delimitations
This inquiry was limited to the perceptions of Cameroon WCBAs regarding access to
healthcare services. The study focus arose from findings indicating that WCBA in Cameroon,

78
particularly those in poor rural communities, have limited access to healthcare facilities and services
that cater to their healthcare needs (World Bank, 2013). Despite a growing need for a sustainable and
affordable healthcare system that meets the basic healthcare needs of WCBA who need medical care,
a gap persists in understanding the reasons behind inaccessibility issues and how such issues have
influenced the personal satisfaction and health-awareness frameworks that do exist. Although
researchers suggested that the health of WCBA in the southwest region of Cameroon is of great
concern, there was however, limited data about how women in these regions perceive their health and
healthcare access. The lack of information on how WCBA in this region perceive healthcare access is
the rationale for focusing on this study.
The screening process for study participants excluded women under the age of 18, as they are
considered minors and unethical. The study focus was on WCBA in Cameroon 13 to 45 years of who
have experienced childbirth and access to healthcare. Additionally, given the characteristics of the
sample size, it may have been too small or homogeneous to make accurate generalized findings to
other similar population out the scope of this study.
Significance of the Study
This paper has crucial implications for healthcare policy formulators in Cameroon. By providing
information that is pertinent to examining and evaluating the situation of healthcare in different parts
of the country, especially in rural areas, healthcare policy formulators have grounds for revising
standing guidelines, and where necessary, introduce new ones to improve the level of healthcare
services. The second theoretical contribution of this paper was expanding existing literature. As noted
earlier, little research exists on the topic, especially regarding the scope of study. Although there is
research evaluating the status of healthcare delivery in developing countries, little research addressed
the identified target population in Cameroon. This study provided information about this segment of
the population through their lived experiences.

79
Summary
Access to healthcare in most countries in the global south continues to be a challenge and
disproportionately affects WCBAs (Imo et al., 2016). This problem is exacerbated in poor and rural
communities in these countries with limited resources, including Cameroon (Phung et al., 2014).
Despite the growing need for a sustainable and affordable healthcare system that meets the basic
healthcare needs of WCBAs who need medical care, a deficiency of investigation persists regarding
how WCBAs seeking healthcare services perceive healthcare access through their lived experiences
and access of the existing healthcare system in Cameroon.
This descriptive phenomenological study allowed WCBAs an opportunity to express their
opinions about their experiences when seeking healthcare services in Cameroon. Chapter 1 provided
an overview and background of healthcare access for WCBAs in Cameroon, in addition to the problem
and purpose of the study, nature of the study, and research questions. Chapter 1 also explored the
significance of the study, highlighting implications for positive social change.
Chapter 2 will provide a review of the extant literature on Cameroon, access to healthcare, equity of
women’s health status, barriers to healthcare access, maternal and reproductive health, maternal-child
morbidity and mortality among pregnant women, and a summary. Chapter 3 will describe the
methodology for the study, including justification for the phenomenological approach, role of the
researcher, data collection and analysis, and ethical considerations. Chapter 4 will describe the results
of the data collection, including quotations from participants about their experiences and viewpoints.
Chapter 5 will conclude the study, providing an interpretation of the results and suggestions for future
research and practice.

80
Chapter 2: Literature Review
Introduction
The purpose of this qualitative study was to examine how WCBAs seeking physician services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. Also, this study discerned how WCBAs perceive the overall process of access to healthcare
institutions. Examining how WCBAs in Cameroon perceive the quality of the healthcare services
offered and how this impacts their quality of life is significant. Cameroonian WCBAs living in rural
communities are most impacted by lack of services due to poverty, low income levels, lower levels of
education, and poor infrastructure (Kruk et al., 2010). Although the need for improved access to
affordable healthcare services for WCBAs has existed for a long time, little has been documented
regarding the perceptions of this population regarding healthcare access and quality of care.
Cameroon is located in central Africa, with an estimated population of 21.7 million living in
475,442 square kilometers (Nzima Nzima, 2014). The overall region contains 58 districts, 360
subdistricts, and 339 councils (Tandi et al., 2015). Cameroon was ranked 150th of 187 countries on
the Human Development Index in the 2014 Human Development Report, having scored 0.512 on a
scale of 0 to 1; Cameroonians have a life expectancy of 55.5 years (Nzima Nzima, 2014). Specifically,
the country is located at the bottom of the Gulf of Guinea and is surrounded by Nigeria, Chad, Congo,
Gabon, Guinea, and Central African Republic. The public healthcare sector of Cameroon follows the
regional delegations of health and health districts comprising of tertiary, secondary, and primary
healthcare delivery services.
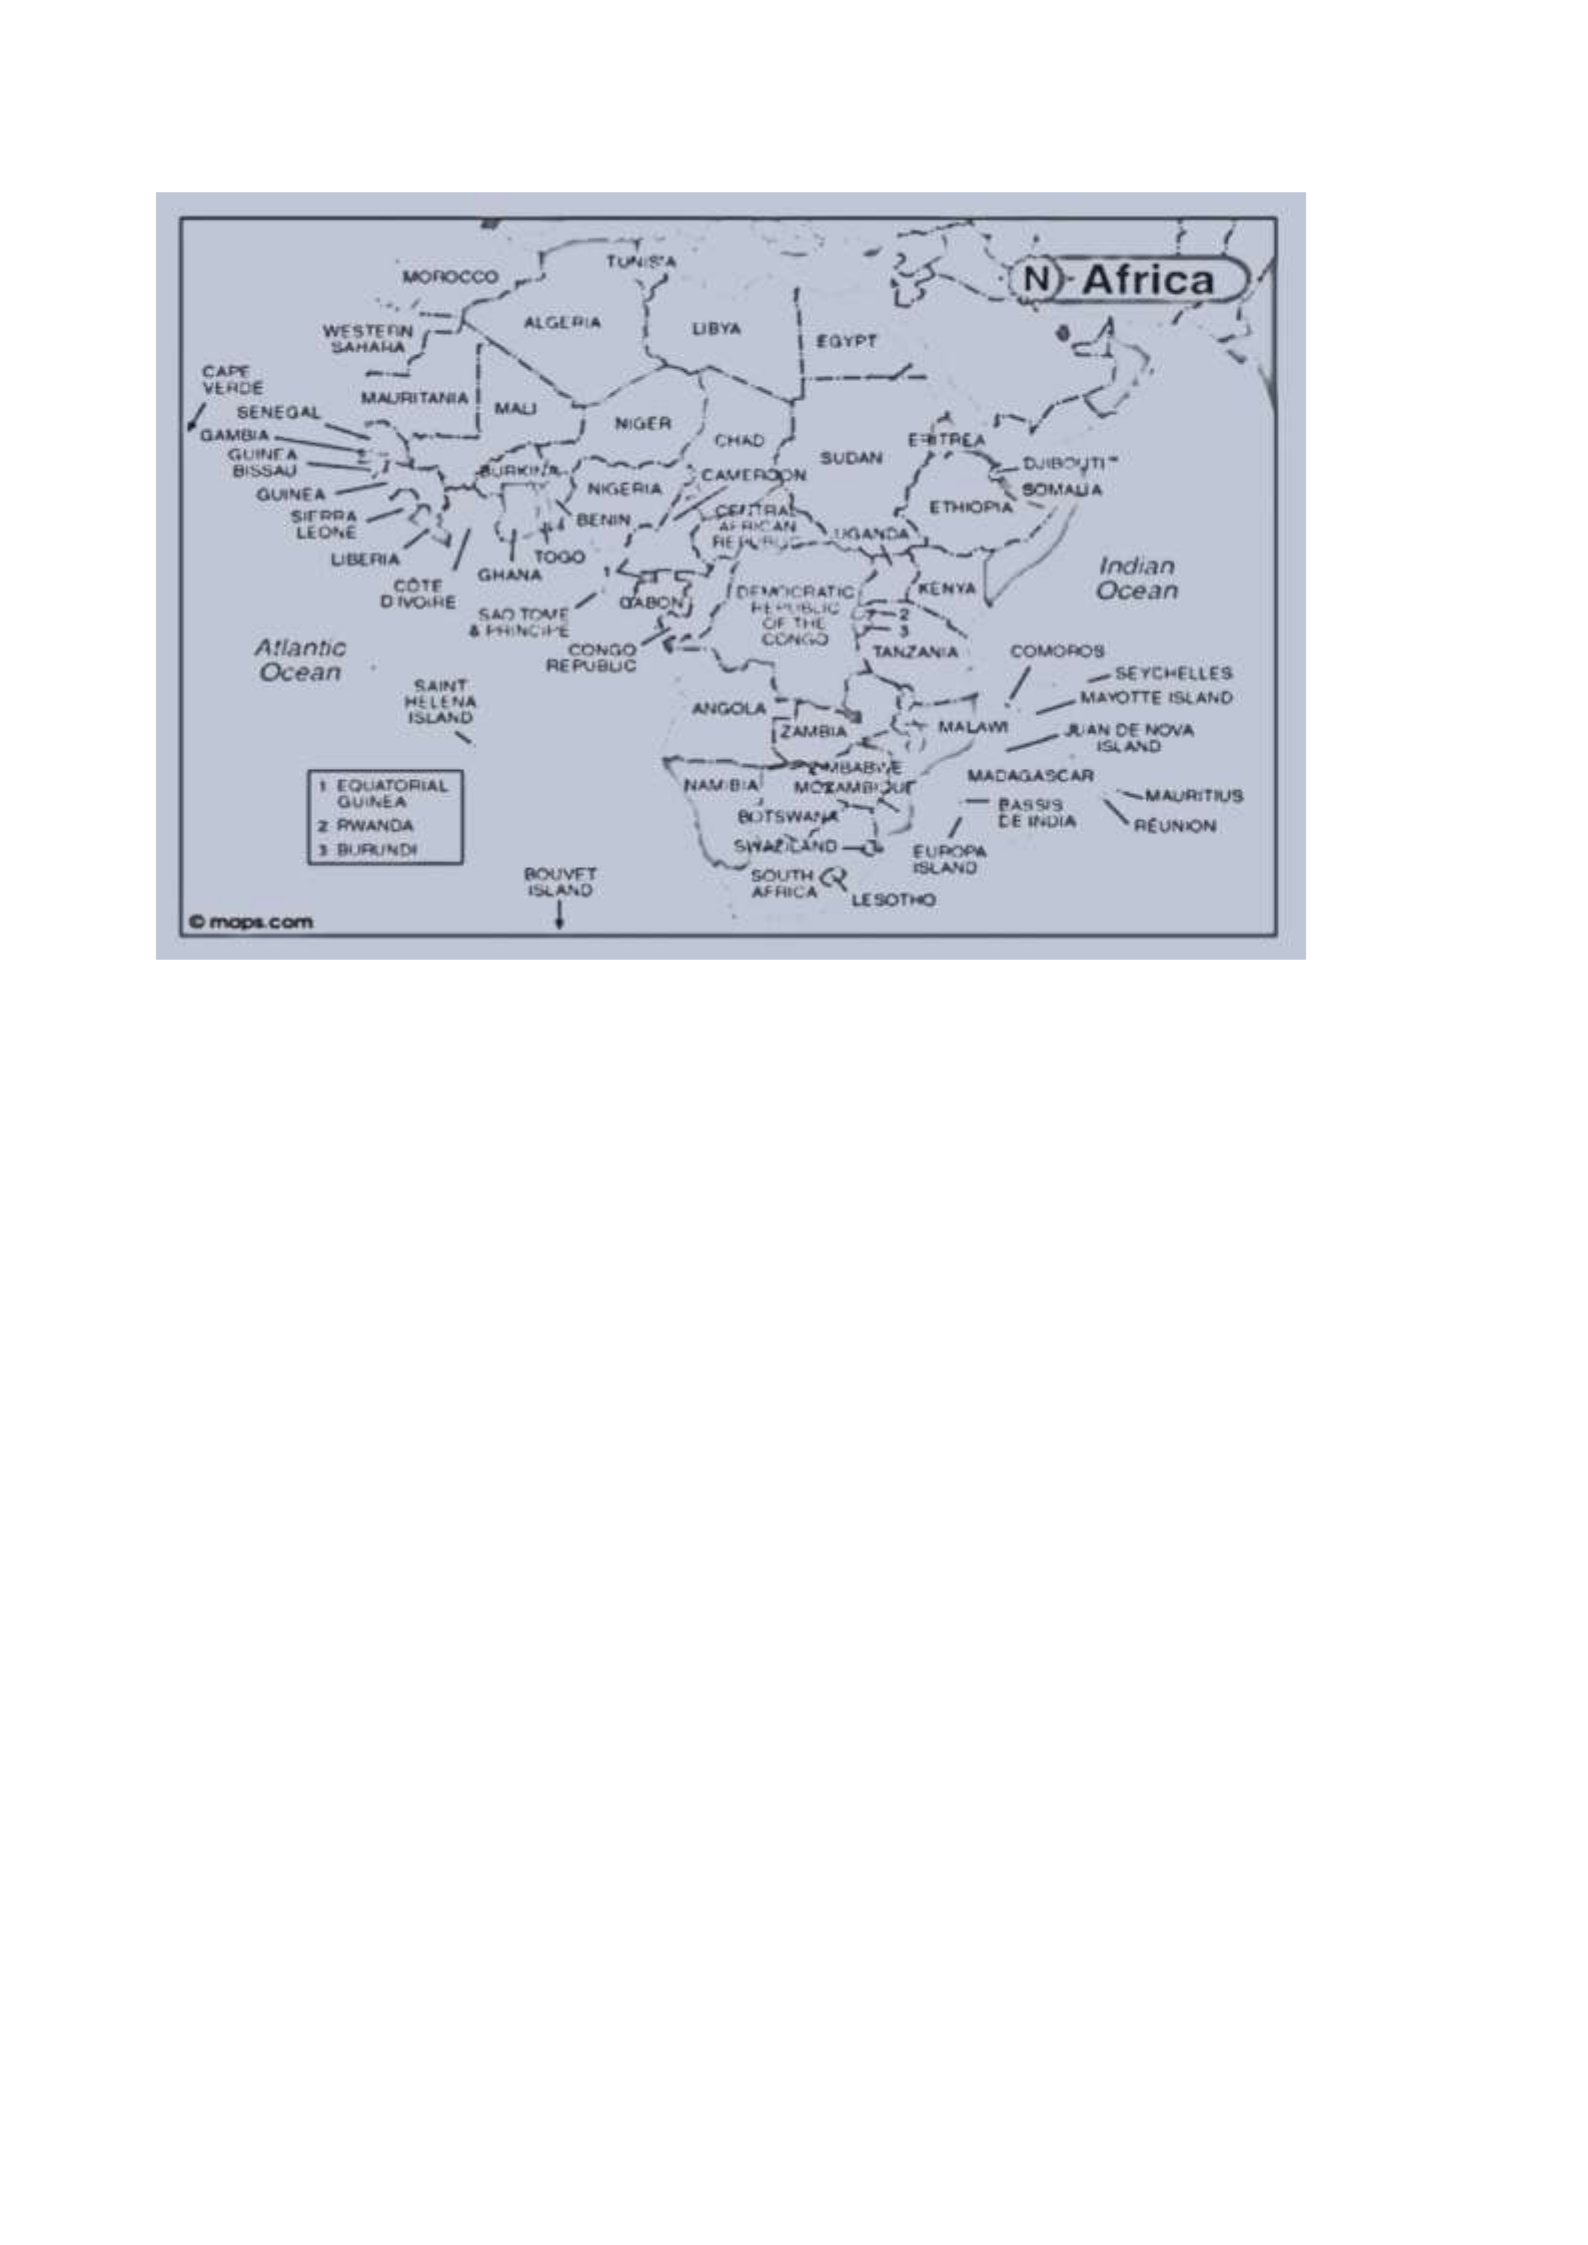
81
Figure 2. Map of Africa describing geographical location and healthcare structure (Egbe, 2014).
Literature Search Strategy
This study used five major library databases to conduct the literature review: ProQuest
Research Library, PsycINFO, PubMed/Medline, Web of Science, and EBSCOHost. The ProQuest
multidisciplinary library database contains peer-reviewed articles that address several subtopics
related to this paper. PsycINFO mainly contains psychology papers. PubMed/Medline is a medical
library database that contains a few articles related to the research. To provide a wider coverage of the
subtopics, I also used the Web of Science database. The EBSCOHost database contains several articles
related to the topic.
I used two search engines to seek relevant articles and publications: Google and Google
Scholar. The Google search engine is considered one of the most effective tools when seeking content
online. Google Scholar is specific for books, patents, theses, dissertations, reports, and peer-reviewed
articles for academic purposes.
Keywords aligned with the subtopics of the study. Where necessary, I used the names of some
authors

82
who specialized in addressing a specific subtopic. The iteration strategy included reorganizing the
keywords, rethinking the phrases, and seeking fresh articles.
Conceptual Framework
As women of Cameroon possess reduced access to healthcare services, access to healthcare
services in Cameroon is an important topic to discuss. No universally accepted definition of the
concept of access to healthcare exists (Jacobs, Por, Bigdeli, Annear, & Van Damme, 2011).
Stakeholders have different approaches to determining the main variables that influence the topic, as
well as different techniques to measure the level of access in different areas. Peters et al. (2008) said
access to healthcare is “the timely use of service according to the people’s need” (p. 161). Peters et al.
used the way healthcare services are delivered to people as an operational proxy for determining the
level of healthcare access. Jacobs et al. (2011) described four main dimensions of access to healthcare:
The availability of the services, the geographic influences that determine accessibility, the cost that
determines the affordability of the services, and the acceptability of the services among the people.
Barriers to access of care can accrue from the demand side, the supply side, or both sides
(Jacobs et al., 2011). Some major barriers on the demand side are culture and tradition. Social
organizations serve as barriers because they are not making efforts to rectify harmful cultural trends
and traditions (Jacobs et al., 2011). Supply side barriers include factors that hinder the relevant
authorities from providing healthcare services to the community (Jacobs et al., 2011). Some of these
include policies that governs the healthcare system and interventions to increase access to healthcare
services.
The concept of access to healthcare has formed the conceptual framework for several studies
that address healthcare planning. Pemunta and Fubah (2015) noted the concept remains elusive despite
efforts to clarify its multiple dimensions and meanings. Researchers must ensure studies avoid
misguiding professionals and policymakers through biased findings (Pemunta & Fubah, 2015). Their
end product is a comprehensive conceptual framework researcher can use to evaluate and plan

83
activities that relate to a society’s access to healthcare services. Some key components of their
suggested framework are a conceptual model that identifies access as a process that is community-
specific. Nonetheless, the concept of access in the field of healthcare essentially denotes the
availability of appropriate healthcare services whenever and wherever needed by the consumer (Obasi,
2013). In the context of women’s health, therefore, access denotes the ease with which women can use
healthcare services whenever and wherever needed (Obasi, 2013).
Generally, factors such as socioeconomic status, availability of healthcare personnel, sociocultural
practices, and the geographic distribution of healthcare facilities determined the degree to which one
gains access to healthcare (Nzima Nzima, 2014). These factors do so by limiting the affordability,
physical accessibility, or acceptability of healthcare services (Bakeera, Wamala, Galea, Peterson, &
Pariyo, 2009). These limitations result in inequitable health outcomes (Gulliford & Morgan, 2003).
For instance, Low-income individuals report poor health outcomes compared those in high-income
groups. Differences in income often lead to differences in health outcomes.
The concept of access closely relates to the concept of equity, especially with respect to controllable
or
remediable health aspects (Gulliford & Morgan, 2003). Equity is about ensuring all individuals and
groups have equal access to quality healthcare services (Eide et al., 2015). Gender is one factor through
which differences in access to healthcare, or the quality of healthcare, are apparent. Gender polarity is
particularly true for developing nations like Cameroon, where women have poor access to basic health
services such as maternal health services (Sheikh et al., 2015). Differences in health outcomes are
even more pronounced among
WCBAs, who have unique health needs. Income levels magnify these differences (Sheikh et al., 2015).
Healthcare access is, therefore, an important indicator of the soundness of a healthcare system.
Equity
Equity in the distribution of healthcare services is another reason for the poor health status of
Cameroon;

84
hence, it is important to discuss equity. Health equity is the principle underlying a commitment to
reduce, and ultimately eliminate disparities in health and in its determinants, including social
determinants. Pursuing health equity means striving for the highest possible standard of health for all
people, and giving special attention to the needs of those at greatest risk of poor health, based on social
conditions (Braveman, 2014). The particular aim of doing this is helping societies focus on physical
health, measured by elements such as mortality and well-being. The need to improve the health status
of the most vulnerable populations drives the importance of equity in health. Disadvantaged groups
across the globe have the least chance of survival when attacked by disease (Whitehead, 2014). In
addition, large gaps in mortality exist between urban and rural populations in various countries. In
many cases, rural populations performed poorly in access to quality healthcare when compared to their
counterparts in urban areas (Whitehead, 2014).
The concept of equity in healthcare has also received a fair share of theoretical adjustments
through the years to guide operationalization and measurement (Braveman & Gruskin, 2003), aimed
at helping achieve a modern society. Braveman and Gruskin (2003) said that “equity in healthcare is
the absence of systematic disparities in health between groups with different levels of underlying social
advantage/disadvantage” (p. 1). The advantages and disadvantages that determine the level of
healthcare include power, wealth, and gender (Braveman & Gruskin, 2003). Other operational
elements that determine differences in equity include racial, ethnic, and religious factors (Braveman
& Gruskin, 2003).
Women’s Health Status in Cameroon
For women, especially those of childbearing age (15–45 years), the significance of access to
healthcare
services cannot be overemphasized. These services range from maternal health services (prenatal,
child birth, neonatal, and postpartum care) to services relating to family planning, reproductive-tract
infections, sexually transmitted diseases (STDs), and gynecological cancers (Obasi, 2013). Without

85
adequate access to these services, women are more prone to complications such as death (of the mother
or infant) during childbirth,
STDs, unwanted pregnancies, and cancers (Obasi, 2013). Lack of access can significantly affect
women’s ability to execute their caregiver roles (Weinger & Akuri, 2007).
Generally, Cameroon has one of the most deplorable healthcare systems in the world, taking the
150th
position of 187 countries in the Human Development Index (Nzima Nzima, 2014). In addition, the
country has a life expectancy of 53 years of age for men and women, and an incidence rate of 24% for
communicable diseases, which is the second highest in the region (World Bank, 2013). Although
measures such as life expectancy and the prevalence of communicable diseases provide valuable
insights about the health status of the general population, they do not consider the significant
differences between the health status of men and women (Obasi, 2013). The patriarchal nature of
societies in Africa places hardships on women that negatively affect their health (Weinger & Akuri,
2007). It is imperative to consider health-status measures specific to women when considering access
to healthcare services. Some measures could include maternal mortality rate, infant mortality rate,
fertility rate, contraceptive prevalence rate, skilled-birth-attendant rate, and frequency of prenatal care
visits.
In Cameroon, the mortality rate for children under the age of 5 is 127 per 1,000 live births (compared
to
107 for Africa and 51 globally), whereas the maternal mortality rate stands at 602 per 100,000 live
births (compared to 480 in Africa and 210 globally; UNICEF, 2011; World Bank, 2011). These high
rates of mortality are often caused by factors such as prepartum and postpartum hemorrhage,
inaccessibility to prenatal and postnatal care, and inadequate access to antibiotics (Obasi, 2013; Tita,
Selwyn, Waller, Kapadia, & Dongmo, 2005). Additionally, skilled healthcare workers do not attend
40% of all births in Cameroon, the contraceptive prevalence rate is below 30%, and a 20% unmet need
persists for family planning (World Bank, 2011). The statistics for skilled birth attendance and unmet

86
need for family planning closely match those of peer developing nations where 45% of women give
birth without trained attendants and 23% of women of childbearing age have unmet family-planning
needs (Obasi, 2013).
Such egregious health indicators clearly showed that access to healthcare is a major challenge
in Cameroon, with women most highly affected. For instance, the high maternal-mortality rate shows
that access to and quality of neonatal and obstetric care remains a major challenge in the country
(World Bank, 2011). Additionally, the low contraceptive rate implies that WCBA are prone to not only
unwanted pregnancies, but also STDs (World Bank, 2011). More importantly, giving birth without
trained attendants implies women are not in a position to manage or prevent likely birth complications
such as postpartum hemorrhage (Obasi, 2013;
Tita et al., 2005). Therefore, it is imperative to consider the factors that hinder access to healthcare by
WCBA.
Barriers to Healthcare Access
Like most sub-Saharan countries, a set of factors hindered equitable access to healthcare in Cameron.
These include poverty, the inadequacy of healthcare personnel and facilities, corruption, low per capita
health expenditure, and sociocultural factors (Business Monitor International, 2014; Ibrahim et al.,
2013; Jacobsen & Nielsen, 2014; Maathai, 2011; Poverty and Health, 2013; World Justice Project,
2013). Poverty is a major challenge in gaining access to healthcare in Cameroon (Commeyras, Ndo,
Merabet, Koné, & Rakotondrabé, 2004; Djomo & Sikod, 2012; Parmar & Agrawal, 2010; Soh, 2007).
According to the World Bank (2011), the country’s poverty rate stands at about 40%, with 33% of the
population living on an income below $1.25 per day. The implication is that an overwhelming majority
of the poor are unable to meet the cost of healthcare. This is particularly true for populations living in
the eastern and northern regions of Cameroon, where the increased inflow of refugees from the Central
African Republic has increased competition for the scarce available basic services (Parmar & Agrawal,
2010; UNICEF, 2011).

87
In most poor countries, poverty is more pronounced among women than men (Weinger &
Akuri, 2007). Cameroon ranks 126 of 157 on the Gender-Development Index (World Bank, 2011).
Additionally, girls enroll less frequently in secondary schools than boys (World Bank, 2011). The
implication is that most women are poor and unemployed, and therefore unable to access quality
healthcare. Studies carried out in Nigeria, Ghana, Uganda, Tanzania, Zambia, and the Democratic
Republic of Congo show that the affordability of healthcare services remains a major challenge for
poor women (Ajaegbu, 2013; Nikiema, Haddad, & Potvin, 2012; Obasi, 2013). Millions of women
around the world, the majority of who are from developing countries, die each year from pregnancy-
and childbirth-related causes (Soh, 2013).
Though disparities in health equity in Cameroon operate across gender, it is important to note
that women are the most affected, lacking education and living in rural areas. A report by the World
Bank (2011) indicates that poor women, those without education, and those living in rural areas, have
a higher fertility rate than women in the highest wealth bracket: those with education living in urban
areas. Poor women generally lack information and education about birth control (Obasi, 2013). Lack
of health information is a major barrier to healthcare access in most developing countries (Sheikh et
al., 2015).
Additionally, the prevalence of mother-to-child HIV transmission, malaria, anemia, and
malnutrition is higher in children whose mothers are poor, compared to those whose mothers are more
socioeconomically privileged (WHO, 2012). The greater prevalence of undesirable health status in
poor women results because poor women are often unable to afford user fees even for highly
subsidized healthcare services (Center for Development of Best Practices in Health [CDBPH], 2012).
For prenatal-care services, for instance, most women are unable to attend the four visits recommended
by the WHO, despite immense subsidization of the services by the government (CDBPH, 2012). As a
result, most women are unable to adopt health practices that minimize maternal and neonatal morbidity
and mortality. Failure to attend prenatal visits also may increase the risk of maternal or infant mortality,

88
because health issues like high blood pressure and STDs are not detected and managed sufficiently
early in pregnancy (Obasi, 2013).
Poor women also have difficulty accessing qualified birth attendants and do not pre-natal visits
(Obasi, 2013), which increases the risk of infant mortality, hemorrhage, and other complications that
may arise because of childbirth. In addition, poverty makes it difficult for women to pay for birth-
control services or transportation to a healthcare facility (Obasi, 2013). Poor women tend to place
health concerns low in life priorities (CDBPH, 2012). Poor sanitation, the lack of access to clean water,
poor housing, and undernutrition further complicate the health status of poor women, increasing the
risk of illnesses such as cholera, typhoid, and malaria (Parmar & Agrawal, 2010; UNICEF, 2011;
Weinger & Akuri, 2007).
Cognizant of the needs of WCBA, particularly those living in rural areas, the Cameroonian
government has recently developed initiatives to enhance their economic power and expand access to
reproductive-health information through the Ministry of Women’s Affairs (McTavish & Moore, 2015;
Soh, 2013). Economic empowerment of women and gender equality are crucial for enhancing
reproductive health and the health of women in general (World Bank, 2011). Empowering women in
poor countries represents a significant prerequisite for any substantial enhancement in the access and
use of healthcare services (Obasi, 2013). With better education, greater participation in the labor force,
and better wages, women will be better placed to access information relating to general and
reproductive health as well as healthcare services. Although the Cameroonian government has
demonstrated commitment to empowering women, gender disparities in economic prosperity in the
country remain.
Another barrier to healthcare access in Cameroon relates to the inadequacy of healthcare
personnel and healthcare facilities (Commeyras et al., 2004; Soh, 2007). Reports indicate that two
doctors service every
10,000 people in Cameroon (Poverty and Health, 2013). This ratio is way below the recommended
minimum of

89
23 per 10,000 for physician-to-population ratio, the country’s health statistics are outside the normal
curve (World Bank, 2013; WHO, 2009). While there is no gold standards for assessing the sufficiency
of the health workforce, World Health Organization estimates that countries fewer than 23 physicians
per 10,000 people will be unlikely to achieve adequate healthcare (WHO, 2009). These statistics are
outside the normal curve because of unsuitable living and working environments; for example, salary
cuts have prompted many public health personnel in Cameroon to either intend to migrate or migrate
to other sectors or abroad for better conditions
(Tandi et al., 2015). Additionally, 40% of all physicians in the country practice in the central region,
where only 18% of the overall population lives (World Bank, 2013). As for maternal health, 1.6 nurses
and midwives service 1,000 people (World Bank, 2011), with the nurse and midwife inadequacy more
pronounced in rural areas (CDBPH, 2012). The implication is that WCBA are unable to access quality
neonatal and obstetric care, thereby increasing the risk of maternal complications and death.
Reports further indicated that 18 healthcare providers service 10,000 people in Cameroon,
which is below the 23 healthcare providers per 10,000 people recommended by the WHO (CDBPH,
2012). The scarcity of healthcare providers is a significant problem in Cameroon and the scarcely
available healthcare facilities in
Cameroon are often short of essential drugs, immunization supplies, beds, and medical-emergency
equipment (UNICEF, 2011). As a result, women often do not get quality prepartum and postpartum
care (Obasi, 2013), exacerbated by limited access to specialty services such as advanced diagnostic
and treatment equipment (Morales, Lara, Kington, Valdez, & Escarce, 2002). With the exception of a
few public Mother and Infant Centers that generally provide services to expectant women and those
with children to the age of 3, Cameroon does not have specialized medical facilities that focus on the
health of women (Weinger & Akuri, 2007). The limited availability of specialized equipment explains
why the majority of women with gynecological cancers (cervical, breast, and ovarian) are diagnosed
when the cancers are at an advanced stage (Ako, Fokoua, Sinou, & Leke, 2015).

90
The inadequacy of healthcare personnel and healthcare facilities is further compounded by long
distances to hospitals and the lack of available transportation, which make it difficult to receive timely
treatment (Morales et al., 2002). Particularly in rural areas, patients often have to travel long distances
before accessing a healthcare facility. A study carried out in the Mamfe region of Cameroon
demonstrated that one- third of respondents attended prenatal visits outside their catchment health area
(Edie et al., 2015). Although the Edie et al. (2015) study may not be representative of Cameroon as a
whole, it clearly demonstrates how the geographical distribution of healthcare facilities in the country
hinders access to healthcare services. Large geographical distances reduce the motivation to attend as
many prenatal visits as required (Edie et al., 2015), and cause women to seek delivery assistance from
traditional birth attendants (Kiguli et al., 2009).
Not only women in Cameroon, but also those throughout sub-Saharan countries – Nigeria,
Zambia, Mali, and Uganda – experience problems of long distances and lack of transportation to
healthcare facilities. (Ajaegbu, 2013; Kiguli et al., 2009; Obasi, 2013; Odetola, 2015). These problems
are exacerbated by climatic factors such as rain, which make the already poor roads impassable due to
flooding or muddiness (Nikiema et al., 2012; Obasi, 2013). Due to such difficulties, individuals may
be deterred from travelling to healthcare facilities, electing instead to make use of traditional doctors
(Obasi, 2013).
The problem of inadequate healthcare facilities and healthcare personnel in most developing
countries, including Cameroon, can be attributed to insufficient government expenditure on healthcare
(Center for Reproductive Rights, 2003). Insufficient government expenditure largely explains why the
few available healthcare facilities have limited qualified healthcare workers and is often short of
essential materials such as drugs, beds, and modern medical equipment. Cameroon has the highest per
capita health expenditure in subSaharan Africa, $61 per person compared to $51 for sub-Saharan
Africa (World Bank, 2013). Nonetheless, government expenditure on health is limited and comprises
about 27% of the total healthcare burden, with the rest financed by citizens and international donors

91
(World Bank, 2013). Limited government expenditure on healthcare often implies that women have to
pay for their healthcare services, presenting a major challenge for women (Nikiema et al., 2012). Due
to the gap left by the government in ensuring equitable access to healthcare, nongovernmental and
religious organizations such as the Cameroon Healthcare Access Program, supported by the World
Justice Project, have continued to play a front-line role in expanding healthcare access in the country
(Nikiema et al., 2012).
The high cost of healthcare services, inadequate healthcare facilities, inadequate healthcare
personnel, and limited budgetary allocation present deterrents to the use of healthcare services. These
problems are exacerbated by widespread corruption in public health facilities, which compels citizens
to pay bribes to access medical services that are supposed to free (World Justice Project, 2013).
Negative personnel attitudes, scolding of women, verbal abuse, slapping of women during labor and
delivery, misdiagnoses, excessive wait times, uncomfortable waiting benches, deplorable hygienic
conditions, and embarrassing physical examinations are common occurrences in public health
facilities (Kiguli et al., 2009; Obasi, 2013). Poor quality of care significantly deters women from
seeking help in public healthcare facilities.
As demonstrated in a study of 26 Cameroonian women by Weinger and Akuri (2007), some women
do
not view public health facilities as an available alternative. In another study that sought to examine
pregnant women’s perceptions of prenatal services in Cameroon’s Mamfe Health district, the
perceived quality of care significantly determined the choice of a prenatal site (Edie et al., 2015). A
related study, though not carried out in Cameroon, reported similar findings (Odetola, 2015). One may
elect not to make a prenatal visit, given the perceived lack of benefit or perceived poor quality of
services provided. In alignment, the health-belief model holds that individuals evaluate the benefit to
be obtained from a healthcare intervention against the financial, physical, and psychological costs
involved in using the intervention (Ajaegbu, 2013). If the perceived benefit outweighs the perceived
cost or barriers, the person uses the intervention, and vice versa.

92
The studies particularly demonstrated that perceptions about public health services can
significantly influence the extent to which women use those services. In contrast, Fotso and Mukiira
(2011) demonstrated that women did use public health facilities extensively, especially those from
low-income backgrounds, despite the perceived poor quality of service they offer. The study result
may indicate that poor women often have no option but to use inadequate public services. Studies
conducted in Uganda, though not specifically in the context of women’s health, reported similar
findings (Bakeera et al., 2009; Kiguli et al., 2009). The influence of perceptions on the use of
healthcare services cannot be ignored.
Perceptions originate not only from economic and health-system factors (such as scarcity of
healthcare facilities and personnel, quality of care, and demographic variables such as income and
educational level; Odetola, 2015), but also religious beliefs and sociocultural practices (CDBPH,
2012). Religion and culture can significantly influence the extent to which one uses healthcare
services, particularly for prenatal services (CDBPH, 2012). Women may ignore prenatal visits due to
beliefs and practices that generally discourage the use of modern medicine. The use of traditional
medicine is common in Cameroon, accounting for about 18% of all sources of health services in the
country (Kamgnia, 2006).
Beliefs and sociocultural practices may also affect the extent to which a woman uses modern birth-
control methods (Obasi, 2013), with strong influences on contraceptive use, particularly in developing
countries
(Obasi, 2013). Catholic and Islamic countries have traditionally condemned contraceptives, thus,
women’s use of contraceptives in these countries continues to be markedly influenced by religion and
culture. In Cameroon, about 53% of the population subscribes to Catholicism whereas approximately
22% are Muslims (Center for
Reproductive Rights, 2003). Additionally, Cameroonian women have 4.41 children on average
(O’Reilly, 2010), which is quite high compared to developed countries, where the average fertility rate

93
is less than two children (Obasi, 2013). Therefore, a possibility exists that religion and custom
influence a considerable proportion of women of reproductive age about contraceptive use.
Opinions of men about contraceptives can also influence the extent to which women use birth
control
(Obasi, 2013). In particular, men’s desire to sire many children, their distrust of modern birth-control
methods, and the perceived inconvenience brought about by contraceptive use may dissuade women
from using contraceptives. Additionally, due to fear of their husbands, women may feel afraid to
inquire about or use contraceptives (Obasi, 2013). Women in most patriarchal societies have less
decision-making authority about contraceptive use (Weinger & Akuri, 2007), thereby increasing the
risk of unwanted pregnancies, STDs (Obasi, 2013), and mother-to-child transmissions of HIV
(Nguefack et al., 2016). In some societies, women must seek the consent of their husbands prior to
visiting a health center, and in some circumstances, may not receive such consent (Nikiema et al.,
2012). Marital status and women’s autonomy in making decisions relating to healthcare can
significantly influence the extent to which women seek healthcare services (Odetola, 2015).
Traditional practices often affect not only the use of contraceptives and prenatal services, but
also women’s physical and psychological health (Weinger & Akuri, 2007). Practices such as female-
genital mutilation, early and forced marriage, and delivering children at home are still pervasive in
many African societies to include Cameroon and exposes women to physical torture, but also to
psychological suffering (Weinger & Akuri, 2007)
Maternal and Reproductive Health
In Cameroon, people survived on less than $2 per day (Abrokwah et al., 2016). The Cameroon
government allocates 6% of its budget to healthcare, which is very low for a population of
approximately 23 million inhabitants (Abrokwah et al., 2016). The fee-based system introduced in
Cameroonian hospitals allows medical facilities to charge fees for treatments and services which has
led to many deaths due to lack of medical care when are unable to pay for services (McTavish &
Moore, 2015; Soh, 2013). Women seeking child birth services and who are unable to do so in the

94
hospitals are sometimes compelled to give birth at home with the help of unskilled matrons, thereby
risking their lives and the lives of their children (Soh, 2013). The 2010 World Bank indicators on
maternal mortality in Cameroon suggest that, 700 out of 100.000 women die of pregnancy
complications or childbirth (World Bank, 2013). Childbirth remains a significant risk factor for
mortality where one woman dies every two hours from pregnancy complications or childbirth, and
one pregnancy out of 127 is fatal (World Bank, 2013). This number is alarming, considering that in
most countries in the global south in 2010, this ratio is much lower (World Bank, 2013).
Globally, WHO (2012) recommended that pregnant women obtain at least four prenatal check-
ups by a skilled birth attendant. However, in developing countries women may not be able to obtain
the recommended services owing to a myriad of social and economic challenges. Cameroon has made
significant improvements in reproductive health-service provision. For instance, the percentage of
healthcare delivery service delivery in Cameroon has increased from 26% in 2008–2010 to 36% in
2015 (Schlegel, 2015). However, maternal and child healthcare-service indicators in Cameroon are
low compared to other countries in the global south. Another study indicated that up to 90.7% of
pregnant Cameroonians do not receive all of the recommended prenatal visits attended by a skilled
provider (Woodsong et al., 2014).
Only 67% of WCBA obtained the recommended four prenatal visits, according to WHO standards,
and
only 35% of pregnant women sought professional childbirth services in clinics during January of 2016
(Fletcher et al., 2016). Some factors attributed to such low use of health services across developing
countries include conformity to cultural norms at the personal and community level and the inadequate
and unequal distribution of health resources (McTavish & Moore, 2015). Notable examples include
personal factors; for example, older women tend to seek traditional childbirth methods that contribute
to the low turnout for maternal-health services (Soh, 2015). In addition, the level of education may
influence the awareness of such individuals, whereas religious inclination tends to keep women from

95
seeking maternal healthcare (McTavish & Moore, 2015; Soh, 2013). In addition to the poverty status
of the country, dire environmental conditions negatively affect maternal–child health.
Maternal–Child Morbidity and Mortality among Pregnant Women
The use of maternal–child health services is important in reducing maternal and child mortality, as is
the
achievement of universal reproductive health-services access. In addition to a high mortality rate of
670 per 100,000 children born (Whitaker et al., 2016), 75% of births are performed outside of clinics
and healthcare facilities, and 15% of pregnant women do not receive any prenatal care (McTavish &
Moore, 2015; Soh, 2013). As a result, most pregnant women risk developing prenatal or at-birth
complications that ultimately end up in
fatalities.
Ajong et al. (2016) conducted qualitative research in northern Cameroon and compared the national
mortality rate among children 5 years or younger with the mortality rates of the population that
received health and other community-development programs, including those receiving care and
services from trained health workers and agents, healthcare providers, and community-outreach
programs. Approximately 3,427 women of reproductive age participated in this study. The researchers
surveyed and interviewed the women about the long-term impact of health and other community-based
programs working to reduce infant mortality. The study revealed that programs that combined
community-health outreach with education and sensitization on health promotion contributed to a
sustainable reduction in mortality of children 5 years and younger (Ajong et al., 2016). Cost remained
a significant barrier to women receiving skilled healthcare during deliveries. Only 6.4% of the poorest
women received care from a skilled attendant at delivery, compared to 67.5% of the richest one fifth
of women (Ajong et al., 2016).
Lack of adequate education leaves most of the Cameroonian population entwined in myths about
health

96
and illness. These myths have caused delayed treatments, and in some cases, caused direct harm
(Ajong et al., 2016). Most pregnant women in Cameroon do not seek prenatal care and deliver with
unskilled matrons. Although these matrons are ill-trained and poorly equipped to respond to
emergencies that arise during labor and delivery, many women entrust their lives, and the lives of their
babies, to them (Ajong et al., 2016).
Childbirth educators should consider birthing-environment risks. For most pregnant women with low
socioeconomic status, Cameroon remains a high-risk environment for infant deliveries. At least one
woman dies every minute from childbirth complications; 20 more suffer infection, disease, and injury
(Ajong et al., 2016).
The largest number of these deaths links to hemorrhage and infection, facilitated by generally poor-
quality care. Deaths and disease can be prevented when women have access to efficient health
equipment, services, and trained healthcare workers. The highest percentage of mother–child deaths
occurs during labor and birth and the immediate post-delivery period, accompanied by sepsis and
excessive bleeding (Ajong et al., 2016).
Across the world, approximately 25% of maternal deaths are due to hemorrhage (Ajong et al.,
2016). The onset of hemorrhage is unpredictable and immediate. Without quick intervention,
hemorrhage can lead to hypovolemic shock, succumbing to mortality. Delays in recognizing postnatal
hemorrhage, delays in transportation to health centers, and delays in medical attendance contribute to
the high maternal-mortality rate (Ajong et al., 2016). Infection is responsible for 15% of maternal
deaths (Ajong et al., 2016). Unhygienic environmental conditions that lead to the high rate of mother–
child sepsis could be prevented by implementing sterile environments in health clinics during birth
(Ajong et al., 2016). Basic birth kits can increase the knowledge of perinatal care, aseptic delivery
practices, and infection prevention. Ajong et al. (2016) showed that when birth kits were used in
perinatal care, women and babies fared better. With the use of these kits, the rate of infection was 13
times less probable (Ajong et al., 2016).

97
Summary
The literature review demonstrated that the perception of access to healthcare varied across
communities. Perhaps the most significant factors determining access are economic and social
influences. Clearly, the Cameroon government has taken steps to improve the level of access to
healthcare; however, factors such as the country’s socioeconomic organization and regional
differences in development hinder equal access to quality healthcare. The reviewed works showed that
the level of access to healthcare in Cameroon was below global standards, and key players in
healthcare provision in the country include the government, churches, and traditional formats.
Some key themes emerging from the literature reviewed were women’s perceptions of
governmentsponsored healthcare, the role played by traditional healers, and differences in
socioeconomic development. Few studies addressed these key themes and it is not clear what role they
play in determining the level of access to healthcare by WCBA in Cameroon. The identified gap in
knowledge therefore is the perception of access to healthcare among these women, as influenced by
the identified factors.
This study was designed to fill the identified gap in knowledge. Previously, most information
accrued
from quantitative research studies. This study was qualitative and aimed to answer the research
questions, how do WCBA seeking healthcare services in Cameroon perceive the process of healthcare
access through health institutions? How do WCBA seeking healthcare services in Cameroon perceive
the quality of healthcare services offered through healthcare institutions? How do WCBA seeking
healthcare services in Cameroon understand the impact of healthcare services on their quality of life?
Overall, the study helped determine perceptions of access to healthcare for a vulnerable target
population, WCBA, in Cameroon. Chapter 3 described the methodology used to gather data. Chapter
3 covered justification for the phenomenological approach, role of the researcher, data collection and
analysis, and ethical considerations. The chapter ended with a summary.

98
Chapter 3: Research Method
Introduction
The purpose of this qualitative study was to examine how WCBAs seeking physician services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. The study explored how WCBAs perceive the overall process of access to healthcare

99
institutions. Examining how WCBAs in Cameroon perceive the quality of the healthcare services
offered and how this impacts their quality of life is significant. The research methodology outlined in
this chapter discerns the target population’s perceptions regarding access to healthcare. In this chapter,
I highlighted the methodology I used to address the problem and the purpose of the study. The research
design and rationale, research questions, justification of the phenomenological approach, and role of
the researcher are also explored. I defined the participant selection criteria, instrumentation, data
collection and analysis, and strategies for addressing credibility, transferability, dependability, and
ethical considerations.
Research Design and Rationale
This study was qualitative in nature, seeking to understand the perceptions of Cameroonian
WCBAs regarding access to healthcare. Through a qualitative study, the meaning of the phenomenon
and the experiences of the identified population and their views regarding the issue were the focus.
For this purpose, the approach can be described as “a technique which seeks to describe, decode,
translate and come to terms with the meaning of naturally occurring phenomena in the society” (al-
Busaidi, 2008, p. 175). Phenomenological study research questions aim to uncover and obtain a
detailed understanding of the participants’ lived experiences of the phenomenon under investigation
(Hageman & Frederick, 2013). The following three research questions guided the study and were
critical to understanding the perceptions of WCBAs in Cameroon:
RQ1: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the process
of
healthcare access through health institutions?
RQ2: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the quality
of
healthcare services offered through healthcare institutions?
RQ3: How do WCBAs seeking maternal/child healthcare services in Cameroon understand the
impact
of healthcare services on their quality of life?

100
Justification for the Phenomenological Approach
For this investigation, I used phenomenological techniques to identify specific factors
influencing the phenomenon and characterized the phenomenon by investigating how they perceived
it. The phenomenological approach is important for studying social perceptions, enabling the
collection of deep opinions and insights through constructive means (Smith, 2015). Opinions and
insights are inductive and qualitative, thereby helping establish perspectives. By applying a
phenomenological approach, the experience of the larger population can be studied with high degrees
of accuracy by bracketing a representative sample. This approach builds on a paradigm of personal
knowledge (Smith, 2015); therefore, the validity and reliability of the findings could address the
central objective of the study.
Some specific strengths of the phenomenological approach made it suitable for this study. Most
significantly, the approach enabled the collection of information that is rich in facts, detailed, and
relevant to the human experience (Smith, 2015). Through a critical examination of raw data, it was
possible to determine how WCBAs in Cameroon perceived their current access to healthcare, and
understand how the system affected these women personally and collectively.
Role of the Researcher
Although the role of the researcher is to ensure that the data collected and presented has high
validity, it
is almost impossible to rule out bias. In qualitative studies, bias is the aspect of research that affects
the validity and reliability of the findings (Hibberts & Johnson, 2012). I made concerted efforts to
avoid prejudices and preconceptions, remained objective, and had an open mind when interviewing
participants. Using the reflexivity technique allowed me to address any biases and to remain objective
(Hibberts & Johnson, 2012). Asking the right questions to participants, interviewing the right people,
using appropriate data collection methods, and appropriately interpreting data collected minimized
potential bias in this study.

101
Moderator bias is one of the risks to research validity and reliability. Moderator bias is enabled
by facial expressions, body language, and mode of communication, all associated with the
establishment of rapport between the researcher and participants (Smith, 2015). My personal opinion
was avoided through purposive sampling by applying reflexivity to ensure preconceptions and
perceptions do not influence the overall research process and finding. The other identified significant
bias was biased answering. This aspect is characterized by untrue and partial reporting by participants
(Hibberts & Johnson, 2012). This form of bias was outside the control of the researcher.
Methodology
Participant Selection
I recruited 10 participants from the town of Mamfe, located in the southwest region of
Cameroon. Mamfe is a rural area, located outside the major cities and towns. The system of care serves
smaller populations, has fewer available resources, and provides more healthcare services through
faith-based and nonhealth-related partners and organizations (Varda, Hardy, Millar, & Talmi, 2016).
Qualitative phenomenological studies should contain a sample size between 15 and 20 participants
(Marshall, Cardon,
Poddar, & Fontenot, 2013). For special cases, the size can be slightly higher until a saturation level is
achieved (Marshall et al., 2013). Participants were limited to 10 due to the fewer number of WCBAs
willing to participate and meet the inclusion criteria. Inclusion criteria were that participants were
between 18 and 45 years of age who lived in the town of Mamfe and were able to read, understand,
and speak basic English. WCBAs in Cameroon range from 13 to 45 years of age, but for ethical
reasons, I excluded women under the age of 18, as they are considered minors.
After receiving approval from the Walden Institutional Review Board with IRB #12-17-18-
0325173, I sought permission from the Mamfe, Cameroon local council, and the pastor of the Mamfe
cathedral to recruit study participants. After obtaining permission from the mayor and pastor, I
distributed flyers (see Appendix A) in church on Sundays, where women congregate to worship, and

102
on market days, where women sell and buy food products. I posted flyers in these locations to increase
the chances of more participants seeking to participate in the study. In order to make the source of
contact easier, a local telephone number was included in the flyer.
The participants interested in the study were educated and briefed on the background of the study as
well as include their right to participate or not to participate in the study. I informed participants that
their participation was voluntary and based on informed decisions. Participants were also informed
that they may not have any direct benefit for participating in the study. However, each participant was
compensated $10, or equivalent to roughly 5000 CFA for participating in the study. During the
prescreening sessions, the participants provided me with detailed information, including the times that
they were available for the interview. I scheduled interviews with participants who were eligible and
interested at a date and time convenient for them in a designated office located in a community hall in
Mamfe.
After initial eligibility screening of participants (see Appendix B), I scheduled a face-to-face
interview, which was the primary method of data collection. I greeted participants when they arrived
and established a relationship in an attempt to gain their trust. Participants were asked to sign a consent
form to take part in the study. I sought permission from participants to record the interview process. I
completed the demographic information sheet (see Appendix C) prior to beginning the interview. To
establish accuracy in my methodology and data collection instrument (see Appendix D), I interviewed
the first two participants as a pilot study. This pilot study allowed me the opportunity to minimize
redundancy when the saturation point was reached, test interview questions to allow for accurate data
collection, and practice interviewing. I briefed participants about the nature of the research. Use of the
reflexivity technique helped to remove bias from the research and presented true results.
Pilot Study
In order to establish accuracy of the methodology and data collection instrument (see Appendix D), I

103
interviewed the first two participants as a pilot study. The pilot study helped in testing the quality of
the methodology. A pilot study is a small-scale study through which the researcher can evaluate the
feasibility, effective size, adverse events, time and cost of research (Whitehead, Sully, & Campbell,
2014). Pilot studies also provided an opportunity of testing interview questions and interviewing
practice.
Instrumentation and Data Collection
I collected data by conducting semi-structured interviews. Interviews are the most common
techniques
used to collect qualitative information (Sarantakos, 2012). The duration of each interview ranged from
45 to 60 minutes. Interviews took place in a designated office located in a community hall for privacy
at a time convenient to participants. Participants were allowed to openly share their perceptions about
the current healthcare system of Cameroon.
The goal of semi-structured interviews was to explore and probe interviewee’s responses to obtain an
understanding of the phenomenon under study (Creswell, 2013). This process of interviewing focused
on details of the interviewee’s life experiences and social behavior. Creswell (2013) noted that during
interviews, the interviewer attempts to engage the interviewee in a conversation about attitudes,
interests, feelings, concerns, and values as they relate to the research topic. I recorded the contact
information for participants for the purpose of following-up. Member checking technique allowed
participants the opportunity to review their statements for accuracy after the interview to increase the
credibility of the study (Harper & Cole, 2012).
To participate in the study, participants met the following criteria: Be a woman of childbearing age
(18–45 years), live in the rural community in Mamfe in the southwest region of Cameroon, and be
able to write, read, and speak basic English.
Data Analysis
NVivo 11 and the Colaizzi seven-step process for phenomenological data analysis were used for data
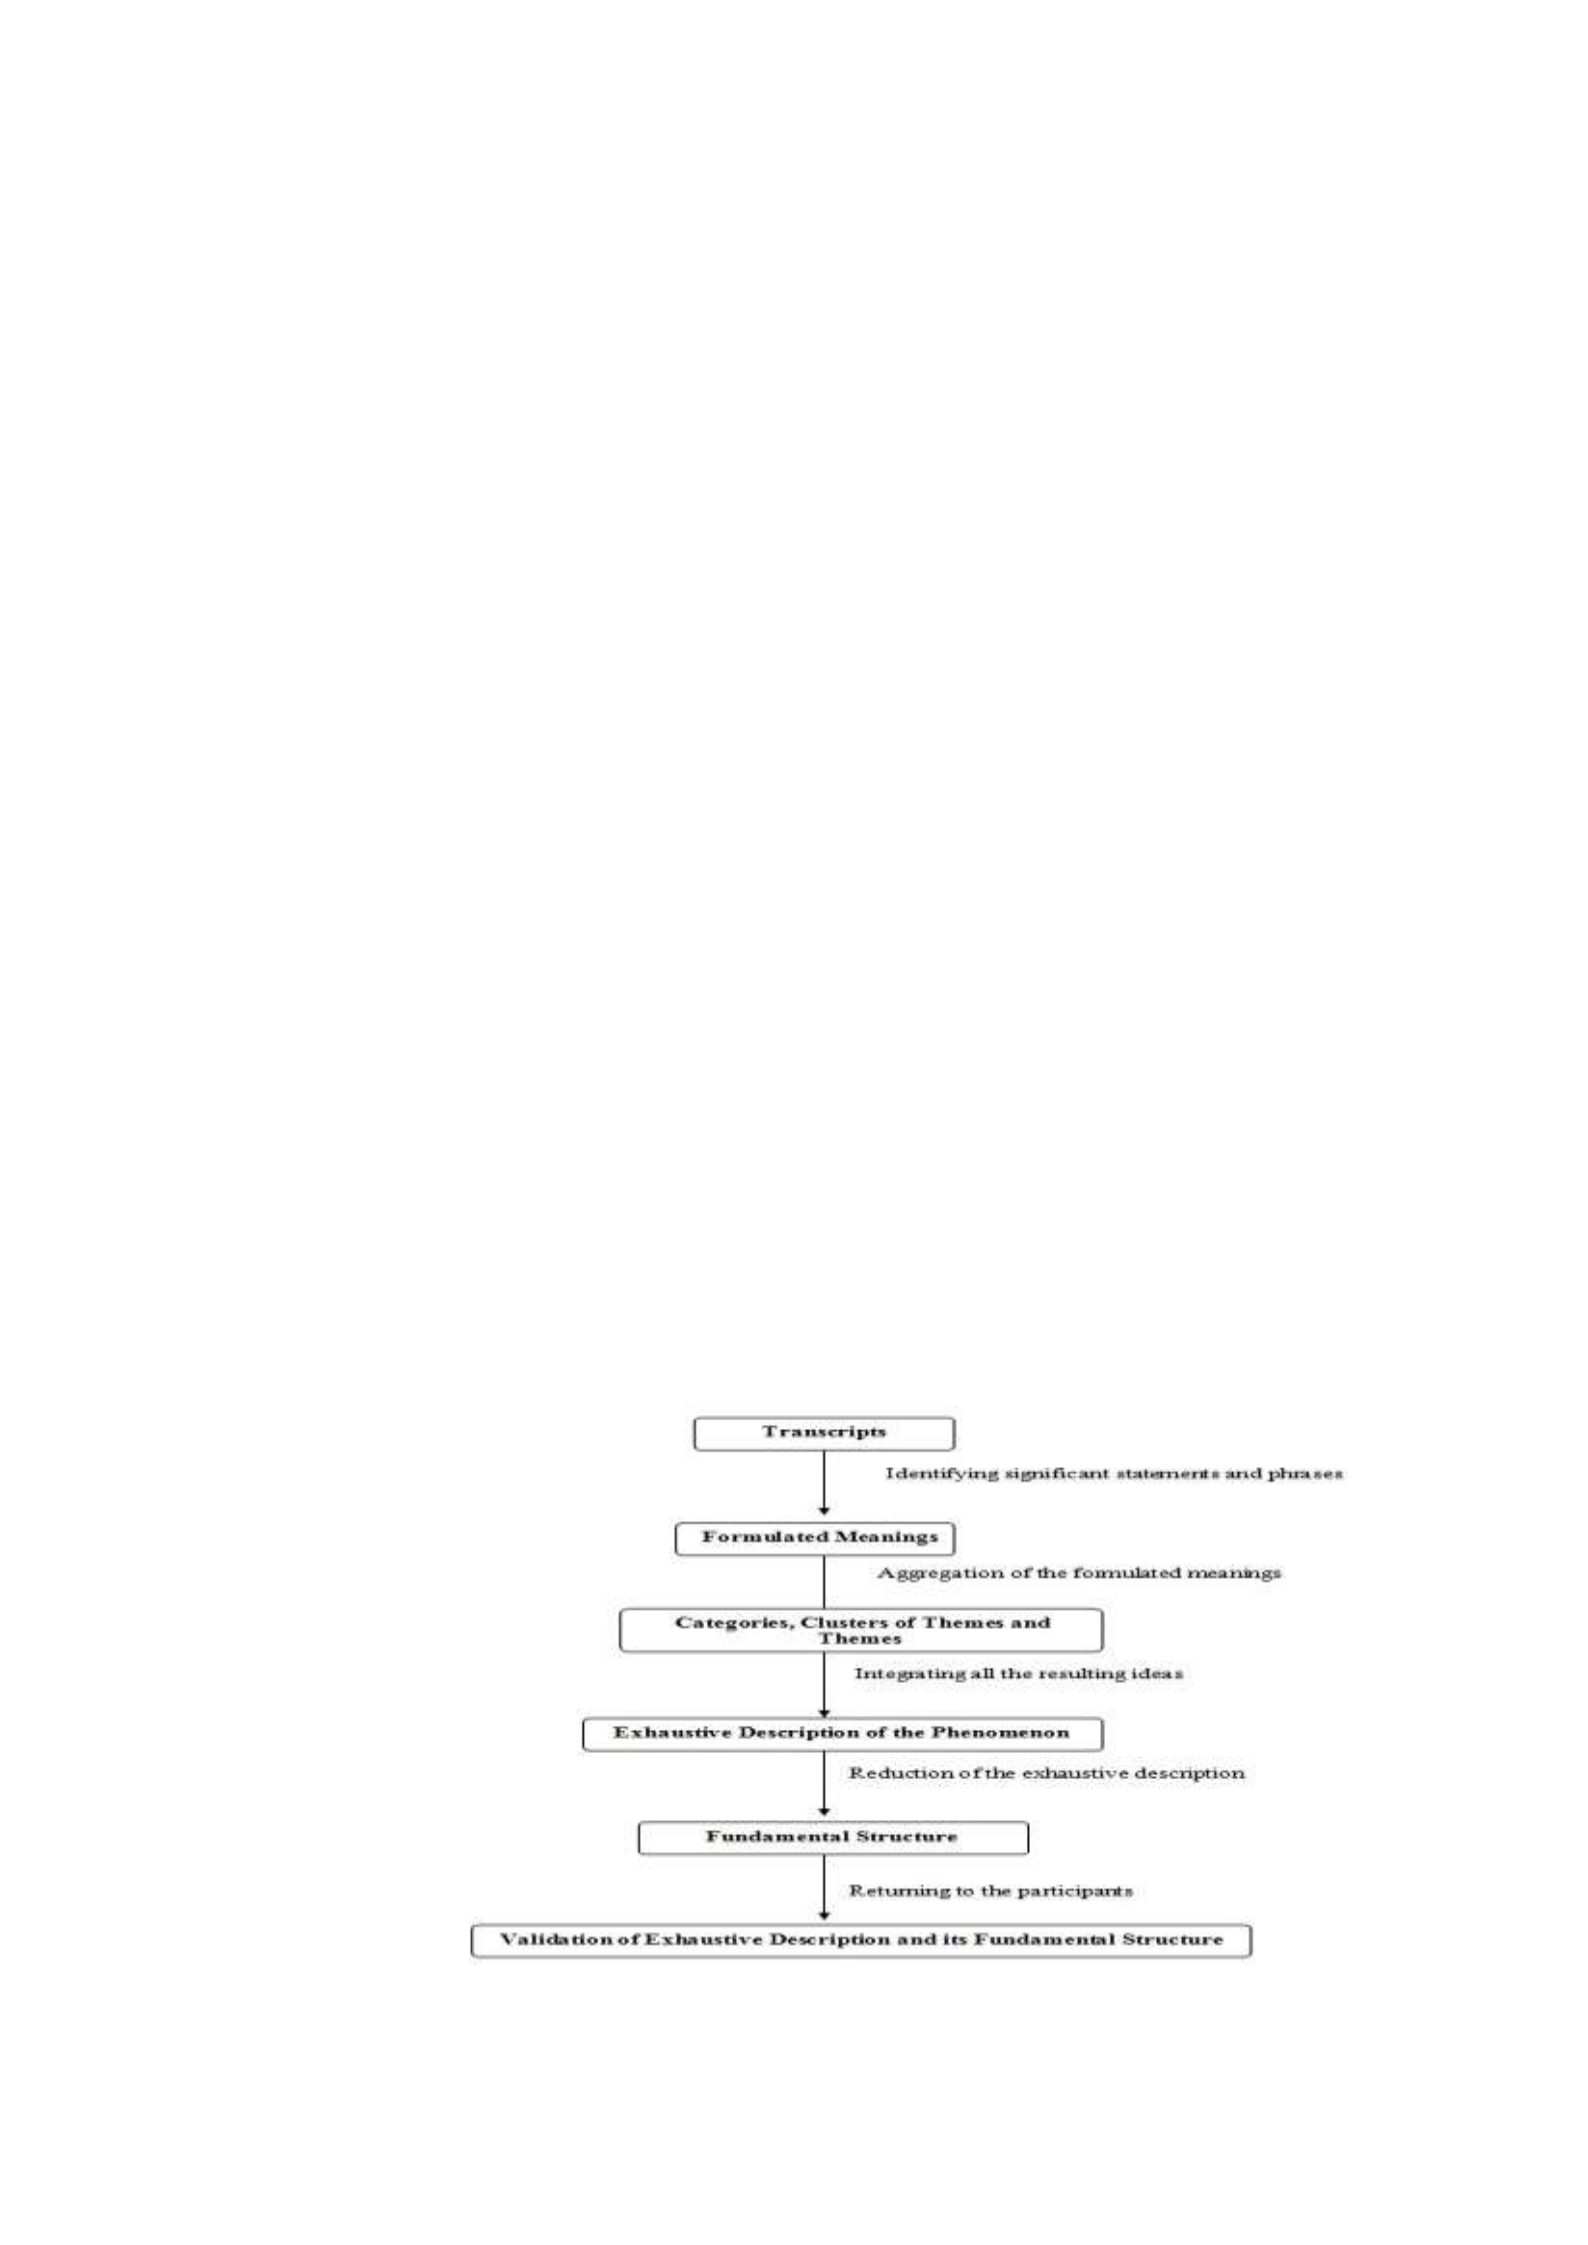
104
organization and analysis. The seven-step process focused on defining concepts and categories (Tesch,
2013). QSR NVivo 11 allowed me to classify, sort and arrange information, and examine relationships
in the data collected (QSR International, 2013). The qualitative data from the interviews were grouped
into themes. The themes were developed based on the objectives identified in the first chapter. The
themes emphasized informants’ responses to particular items in the interviews, and how the issues
they raised related to the objectives of the research.
According to Shosha (2012), using the Colaizzi seven-step process for phenomenological data
analysis allows for comprehensive description and analysis of the phenomena under research. This
study used the Colaizzi process for phenomenological data analysis (as cited in Shosha, 2012) as
follows: I read and re-read each transcript and obtained general knowledge about the content, I
extracted significant statements that pertain to the phenomenon under study from each transcript, I
recorded these statements on a separate sheet, indicating the pages and line numbers, formulated
meanings from these significant statements, sorted these formulated meanings into categories, clusters
of themes, and themes. I integrated study findings into an exhaustive description of the phenomenon
under study, described the fundamental structure of the phenomenon, and sorted validation of the
findings from the research participants to compare the researcher’s descriptive results with
their experiences. (Shosha, 2012; see Figure 3).

105
Figure 3. A summary of Colaizzi’s strategy for phenomenological data analysis. Note. Adapted with
permission from “Employment of Colaizzi's strategy in descriptive phenomenology,” by A. G. Shosha
(2012), European Scientific Journal, 8(27), 34. Copyright 2012 by European Scientific Institute.
Issues of Trustworthiness
To ensure transferability, the external validity of the research was addressed. According to Polit and
Beck, (2013), this is the extent to which the findings of a study can be applied in other situations. This
enabled a more inclusive and overall picture of the topic to be painted. The outcomes of the study were
checked to ensure that they will not be treated in isolation when used by other researchers. All the
processes within the investigation were reported in detail. This enables the works of future researchers
who may follow this paper’s process to be a prototype model. Additionally, all elements of the process
were covered in detail so that other researchers can understand the steps that have been followed.
The first step to ensure the credibility of the study was learning the participant’s culture prior
to data collection. This was achieved through consultations with the mayor of Mamfe rural council
and pastor of the cathedral and also using medical reports and journal information. Through these
ongoing consultations I obtained adequate understanding of the community and its inhabitants.
Second, the pilot study used to test the quality of the interview guide was helpful to ensure credibility.
According to Chenail (2011), the pilot study is a method of testing the quality an interview
guide/protocol for identifying any potential researcher biases and to determine if the intended
procedure performed will be achieved.
To ensure confirmability and dependability, the research methodology was applied throughout the
research process. Confirmability of the research process ensured that the instruments used were not
dependent on human skills and perceptions (Polit & Beck, 2013). To ensure dependability, it is
important that the findings of the investigation were a result of the experiences of the target population
and their independent ideas (Polit & Beck, 2013). It is also important to ensure that the results were
not due to personal opinions. The detailed methodological description of this study helped the reader
of the paper to determine the extent to which the data is constructed and the level of its acceptance.

106
This process was aided by an audit trail, which enables the audience of the study to trace back the
process and make meaning out of the procedures (Polit & Beck, 2013).
Ethical Considerations
For this study, I obtained legal consent to conduct the study from the Walden University’s
Institutional Review Board approval # 12-23-15-0406456. I obtained legal consent from the
Institutional Review Board prior to conducting the study and from the jurisdiction where research was
conducted. Participants completed and signed a consent form demonstrating understanding of the
purpose of the research and allowing researcher to interview them. The main ethical concern for the
study was informing participants about the nature of the study, and having them to agree to participate
in the data-collection exercise.
I kept data collected from the field safely in a locked cabinet in my home office. I stored the
digitally recorded data using a secured computer protected by a password. I included only the
processed and analyzed data in the discussion chapter of this paper and no raw data was shared. After
a post-study period of 5 years, I will destroy hard copies of the raw data by shredding and will
permanently erase the soft copies (in flash drives and other electronic media).
Summary
This chapter outlined the methodological approach for the study. The general aim of the
methodology was to present a systematic process through which relevant data was collected. The study
was a qualitative investigation using descriptive phenomenological techniques to collect field data.
The number of participants were 10, comprising women of 18 to 45 years of age. The data was
collected through face-to-face interviews and was analyzed using NVivo 11 and the Colaizzi seven-
step process to identify themes and subthemes. Interviews were conducted in an office located in a
community hall in the community and the nature of interviews were semi structured. In Chapter 4 the
detail of the demographics of study participants, data collection, study setting, and results were

107
discussed under identified themes in order to explore the impact and perceptions of Cameroon women
about the healthcare services’ quality and access.
Chapter 4: Results
Introduction
The purpose of this qualitative study was to examine how WCBAs seeking physician services
perceive healthcare access through their lived experiences and access to the existing healthcare system
in Cameroon. Also, this study attempted to discern how WCBAs perceive the overall process of access
to healthcare institutions. Examining how WCBAs in Cameroon perceive the quality of the healthcare
services offered and how this impacts their quality of life is significant. The following research
questions were addressed through comprehensive semistructured phenomenological face-to-face
interviews with 10 women of childbearing age regarding their perceptions of access to healthcare in
Cameroon:
RQ1: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the process
of
healthcare access through health institutions?
RQ2: How do WCBAs seeking maternal/child healthcare services in Cameroon perceive the quality
of
healthcare services offered through healthcare institutions?

108
RQ3: How do WCBAs seeking maternal/child healthcare services in Cameroon understand the
impact
of healthcare services on their quality of life?
This chapter includes information relating to the pilot study that follows the main study, study
setting,
demographics of the participants, data collection, data analysis, and study results. This chapter also
includes information pertaining to research quality and trustworthiness.
Pilot Study
I completed a pilot study after receiving approval from the IRB and updating the study flyer (see
Appendix A) and interview guide (see Appendix D) with IRB #12-17-18-0325173. Two participants
were
recruited to take part in the pilot study to ascertain the reliability of the data collection instrument and
quality of the methodology. The pilot study participants were similar demographically to the main
study participants and were treated the same in all ways. Although data from the pilot study is not
usually used in the main study, they were included in this study due to the limited number of WCBAs
willing to participate and meeting the inclusion criteria and because the pilot study participants had no
revisions to the questionnaire (see Appendix B).
The pilot study participants met all eligibility criteria detailed in the study invitation flyer. I screened
participants using the initial eligibility screening tool, and I requested participants to complete a
demographic data form. At the start of the interview, I read the consent form to each participant and
obtained their signature as an indication of full approval and consent to participate in the pilot study.
The two pilot study participants (Megan and Maria) answered all interview questions with responses
that clearly addressed the three research questions. After completion of eligibility screening, I noticed
none of the potential study participants have a first name beginning with an ‘M’. To ensure
confidentiality, I randomly assigned names to participants beginning with the letter M (Madelene,
Margaret, Maria, Martha, Mary, Megan, Melissa, Mercy, Miriam, and Molly).

109
Participants’ responses from the interview confirmed that the study flyer, demographic form,
eligibility screening tool, and consent form aligned with the problem and purpose of the study. It was
telling that participants understood all the study documents, since they did not ask for further
clarification during the recruitment and interview process. Completing the pilot study further enhanced
my interviewing skills, increased my confidence, and prepared me for the main study interviews.
Research Setting
The study took place in Mamfe, located in the southwestern region in Cameroon. I conducted
face-toface interviews with each participant in an office in a community hall to maintain privacy and
ensured participants were comfortable. Prior to the date of the first interview, a member of the Mamfe
rural council gave a tour of the council building and I was introduced to a few staff members present.
My visitors were allowed to use a small waiting area in the lobby with comfortable chairs and a small
coffee table. The council member briefed the receptionist about the study. On the day of the interview,
the receptionist received participants and I was notified by phone of their arrival.
The interview room was small yet, comfortable with a round table and four chairs. I welcomed
participants and allowed them the opportunity to pick a seat of their choice. Prior to the interview, I
spent a few minutes interacting with participants to create rapport and make them feel comfortable
and relaxed. I gave participants $10 (5000 CFA) as indicated in the study flyer and let them know they
did not have to complete the interview before they were compensated. Participants were offered water
and a snack. They proceeded with filling out the demographic checklist and signed the consent form.
I began to administer the interview questions using the interview guide with the participants’ consent.
At the end of each interview, I thanked the participant for participating in the study and escorted them
out of the room.
Participant Demographics
Ten women volunteered to participate in the study. Four of these women, Madelene, Maria, Martha,
and
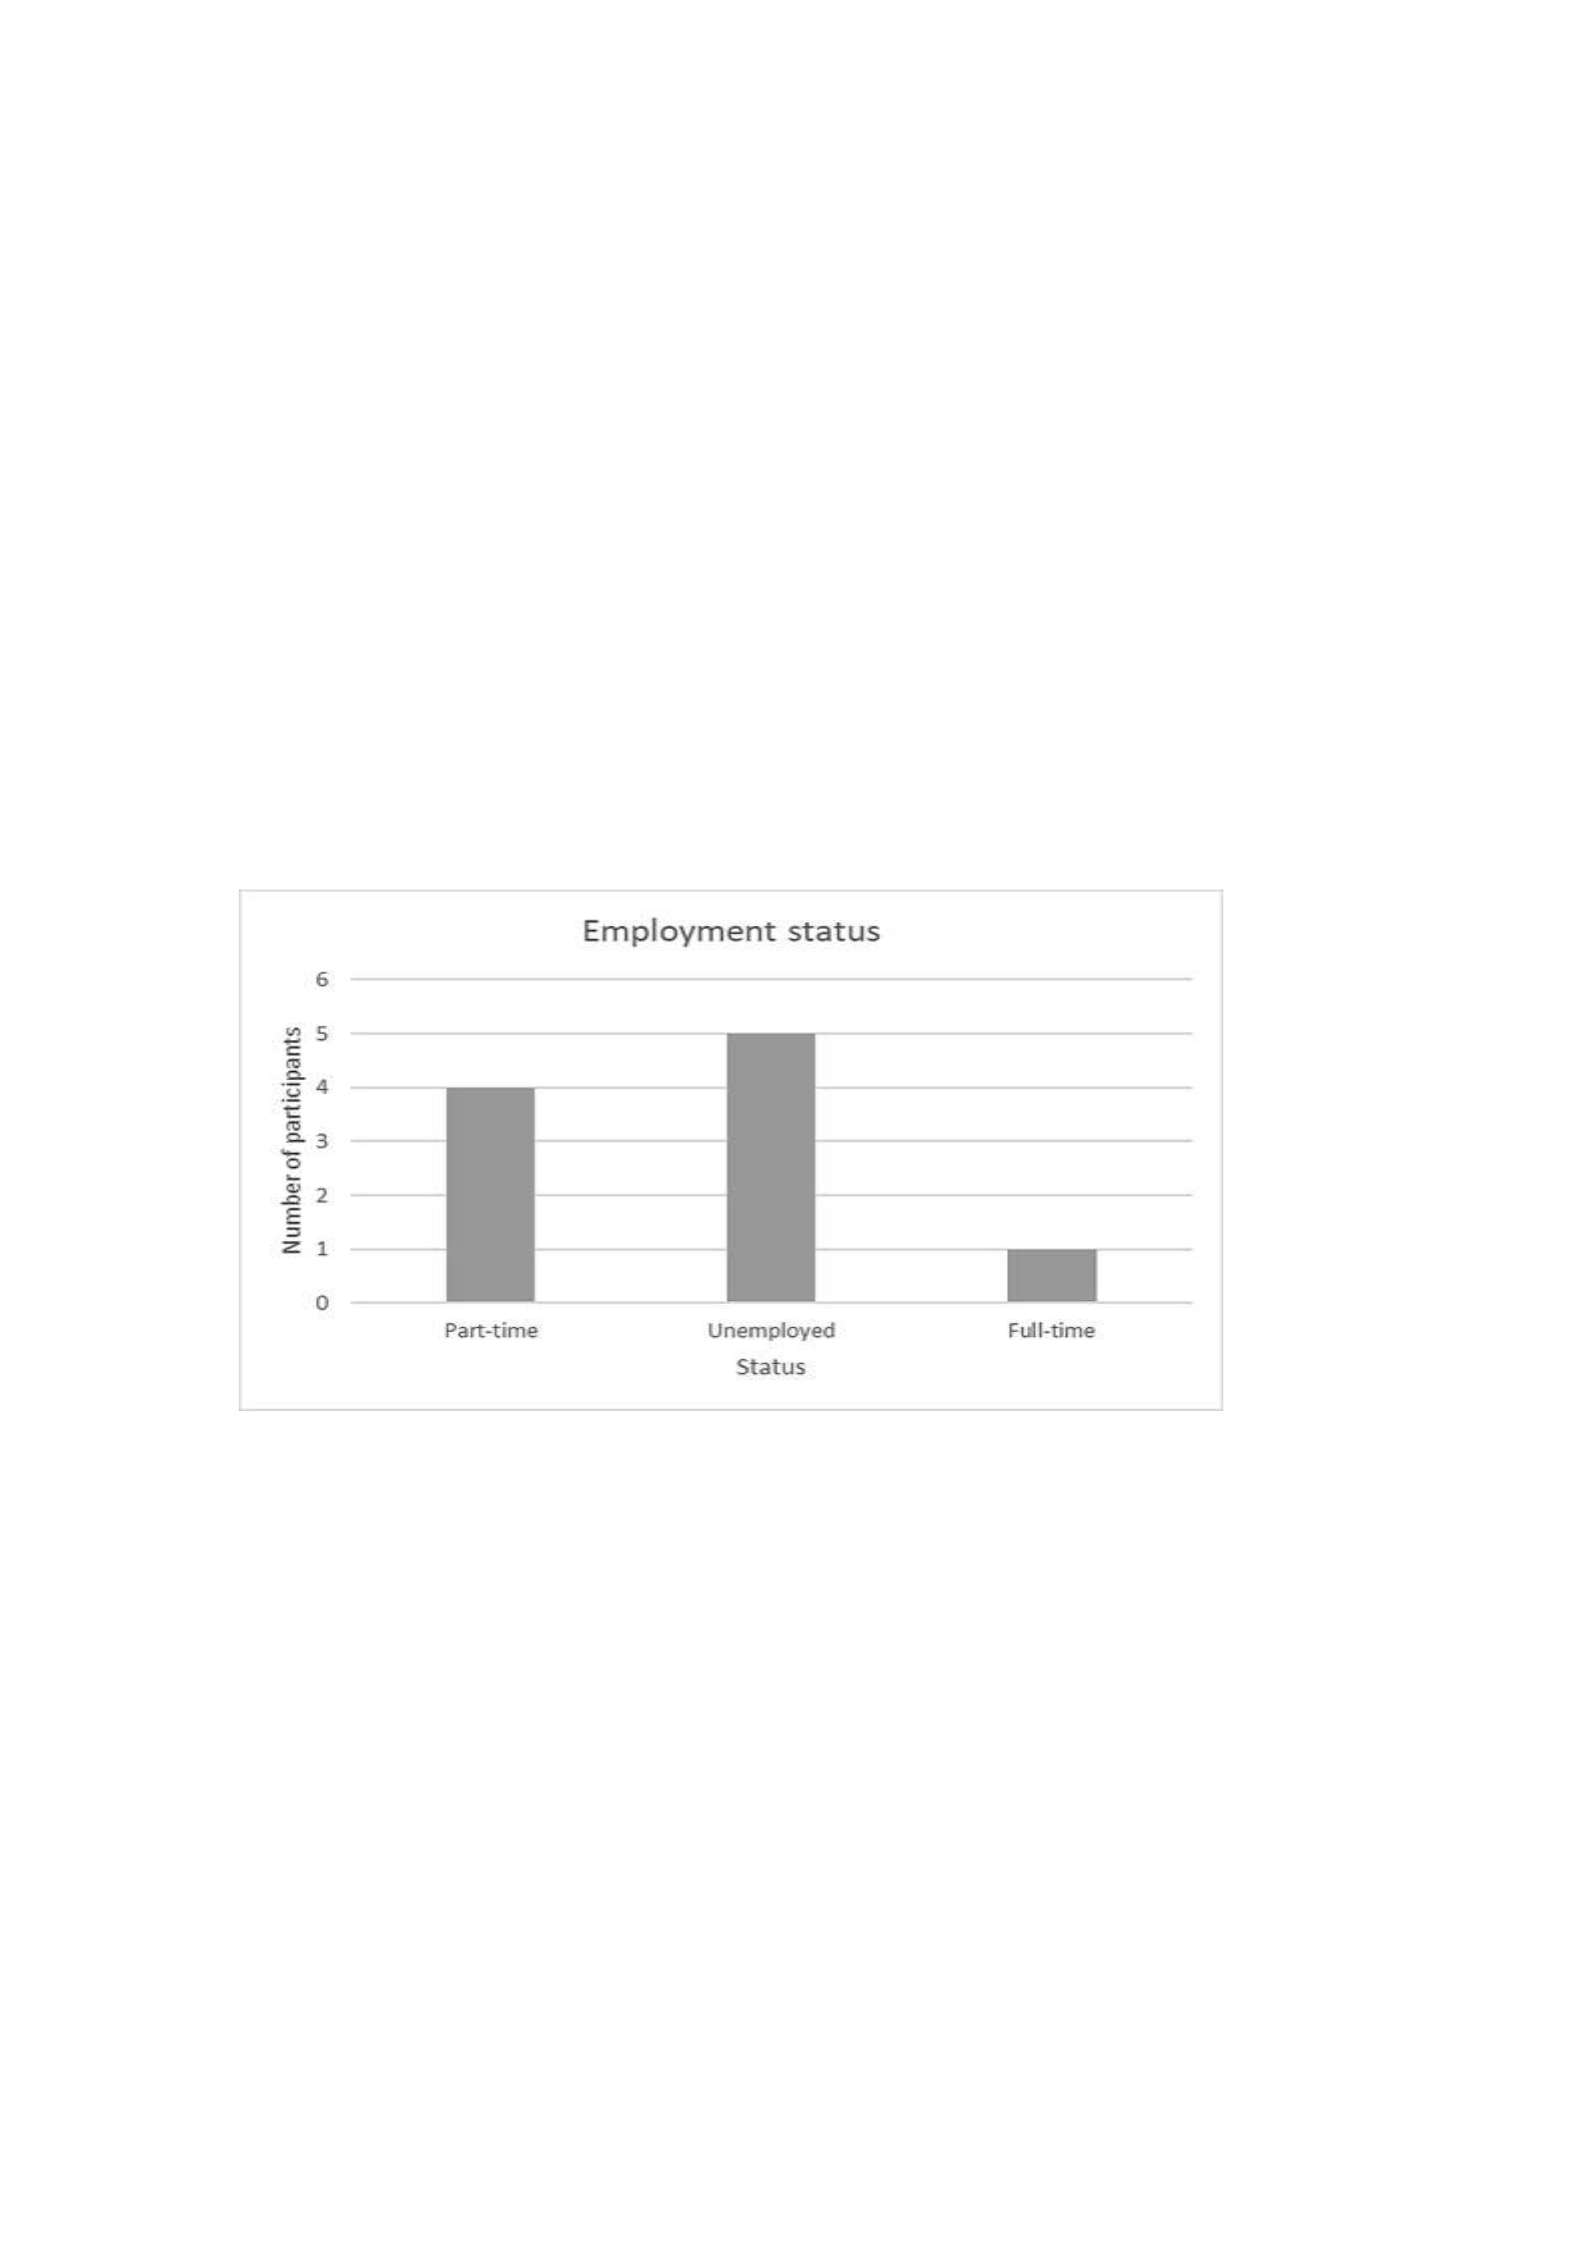
110
Molly, were between 18 and 25, Mary, Meghan, Melissa, Mercy and Miriam were between 26 and 35,
while Margaret was between 36 and 45. Four participants, Madelene, Martha, Melissa, and Mercy,
had less than a high school education, while Margaret, Maria, Mary, Miriam and Molly had a high
school diploma, and Meghan had an associate degree. Nine participants self-rated themselves as low-
income, while Margaret identified herself as having a midlevel income. Five participants were
unemployed (Madelene, Maria, Martha,
Megan, and Mercy). Miriam worked full time, and Molly, Melissa, Mary, and Margaret worked part-
time. Molly was legally separated, Madelene, Maria, Megan, and Mercy were married, and Margaret,
Martha, Mary,
Melissa, and Miriam were not married.
Figure 4. Employment status of the participants.
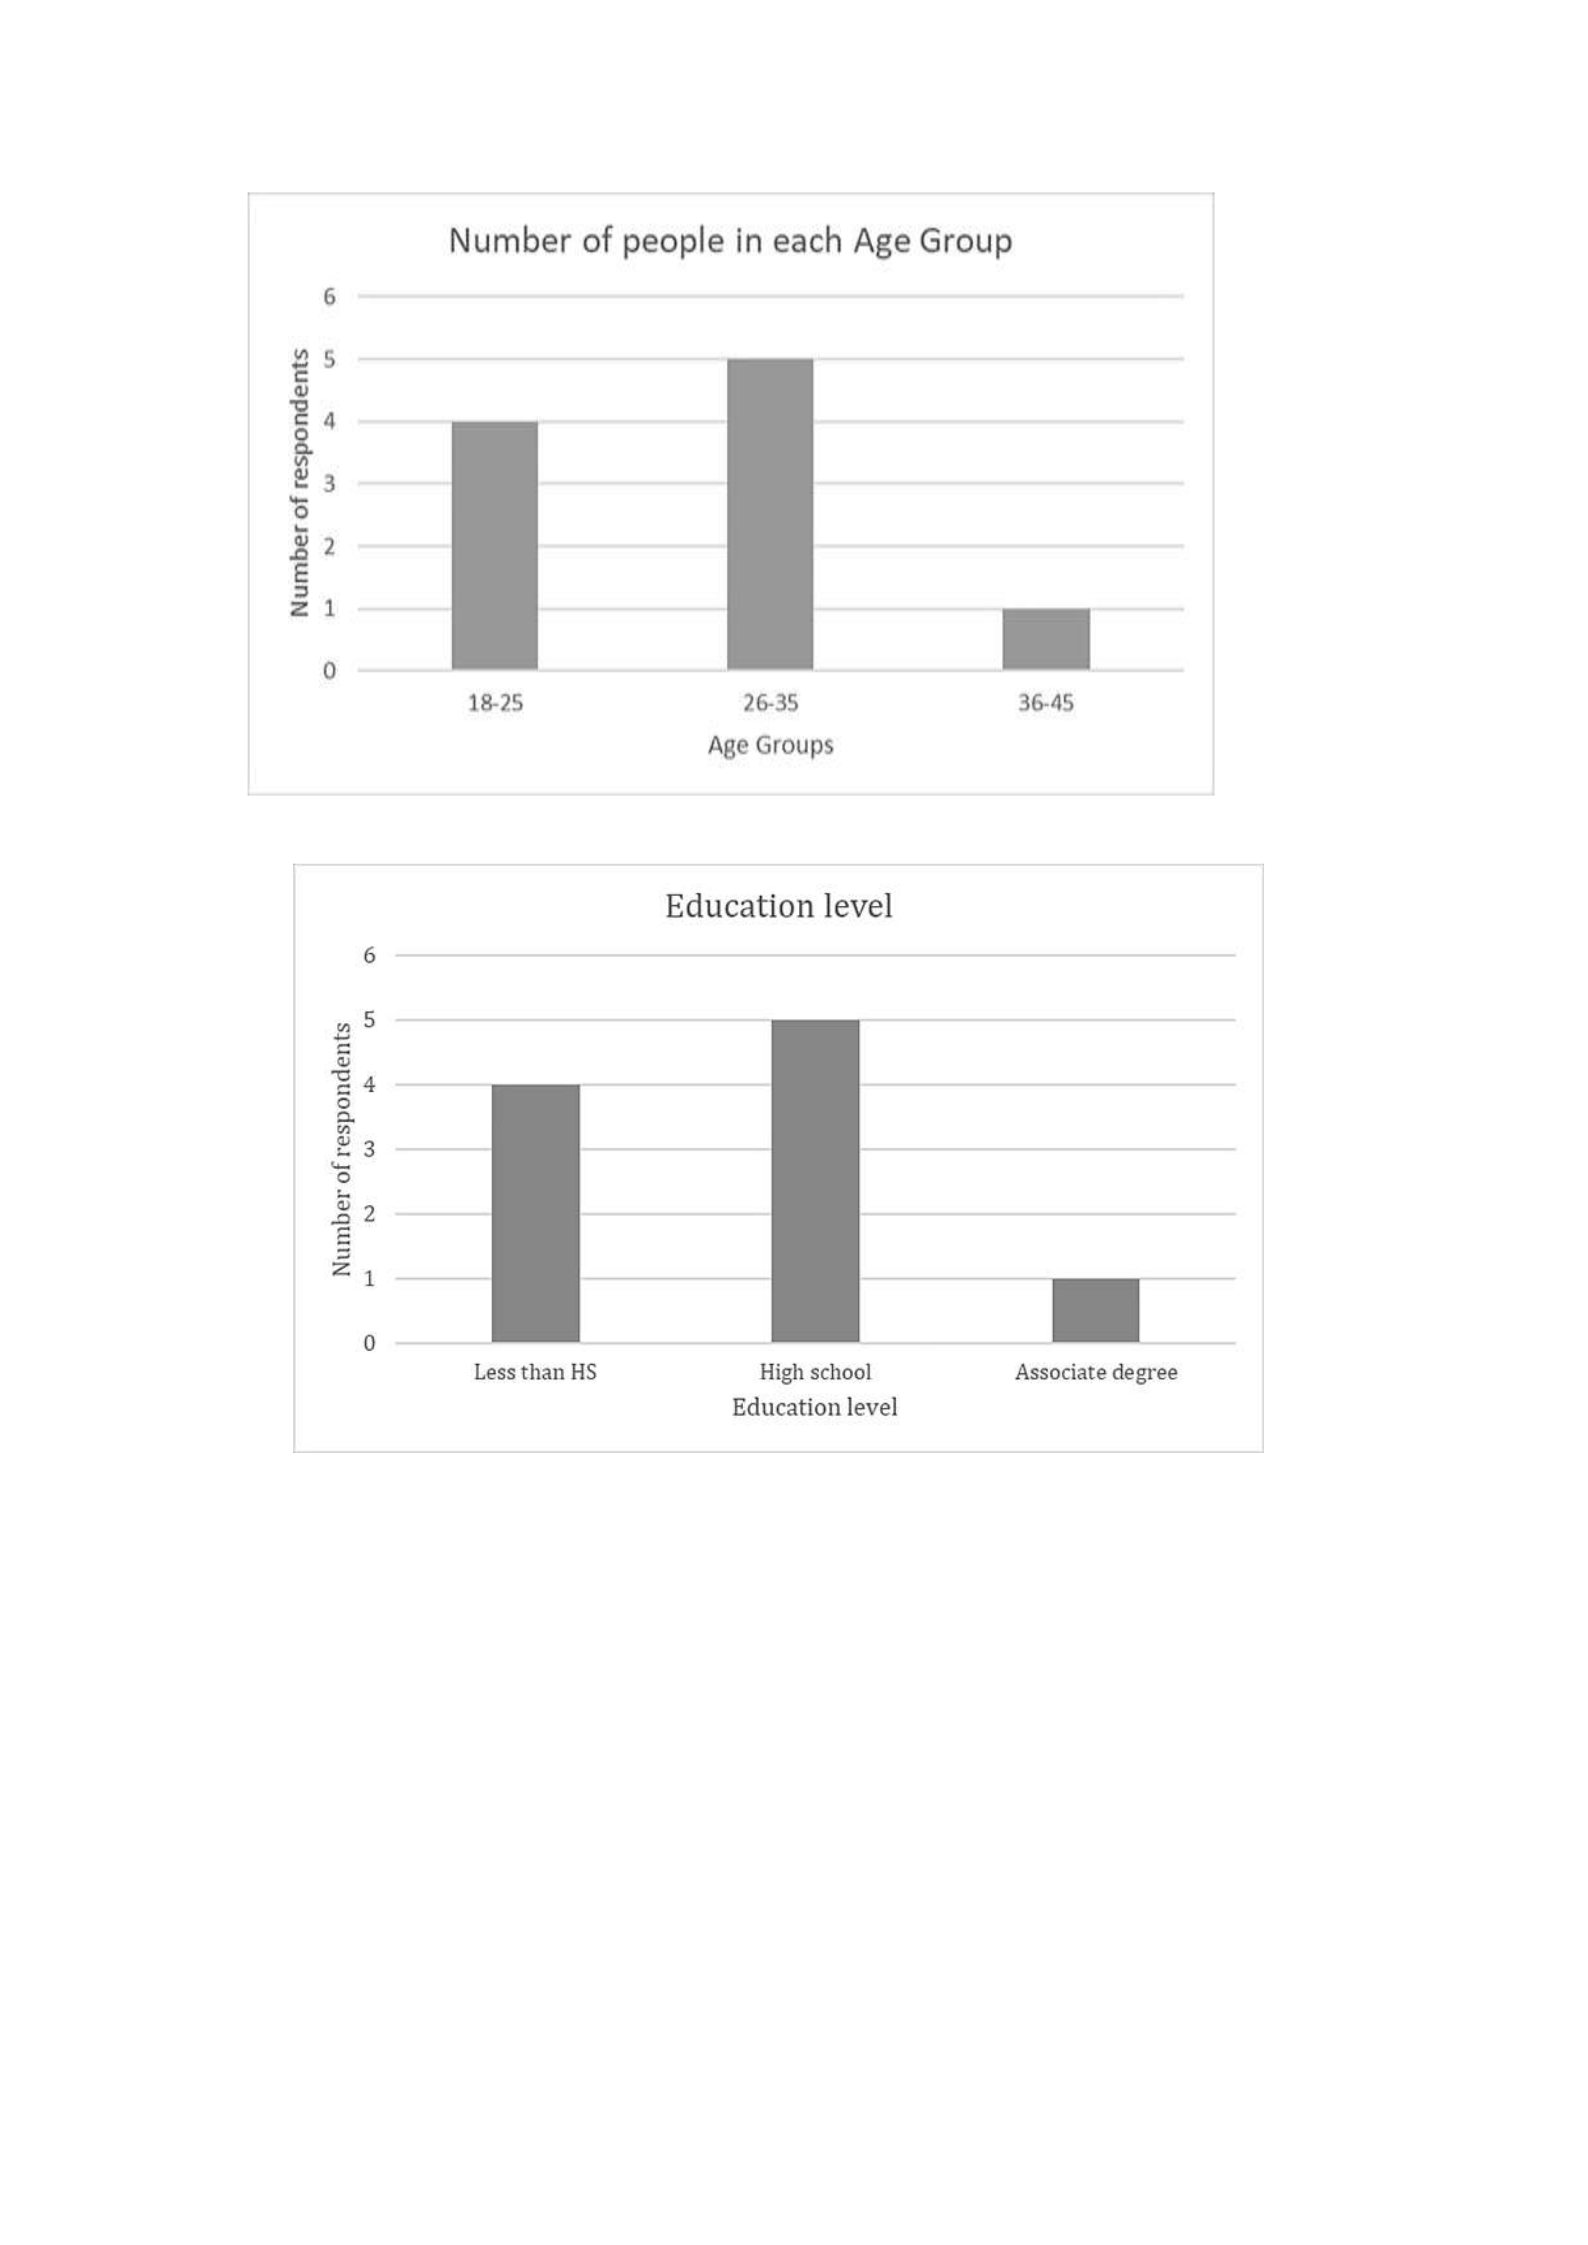
111
Figure 5. Number of participants in each age group.
Figure 6. Number of participants in each education level.
Data Collection
Data were collected from 10 women of child bearing age. These women volunteered their time
and experiences in answering questions outlined on the interview guide (see Appendix D). The
interviews took place between 12/20/2018 and 01/04/2019. The researcher held semistructured
interviews with individual participants in an office in a community hall. The interview sessions lasted
45 to 60 minutes. Participants interested in participating in the study went through the initial screening

112
to ensure eligibility was met. I scheduled a face-to-face interview with participants at a date convenient
for them.
To ensure there was no breach of confidentiality, I immediately downloaded all recorded
interviews from the recording device in a folder on my computer protected by a password. To prevent
data loss, I also saved interview data on an external hard drive protected by password. I transcribed
interview recordings into word document using the same computer to enhance data security. The
recording device and all notes are stored in a locked cabinet in my home office.
Evidence of Trustworthiness
Member checking was used to establish the credibility of the data. The researcher contacted the
participants after the data collection period to check and confirm that the data were indeed what they
had said during the interviews. The pilot study used to test the quality of the interview guide was
helpful to ensure credibility. As posited by Chenail (2011), the pilot study is a method of testing the
quality of an interview guide/protocol for identifying any potential researcher biases and to determine
if the intended procedure performed will be achieved. The researcher constructed an audit trail during
the research process and was always aware of personal biases that may have influenced the study
To ensure transferability, the external validity of the research was addressed. According to Polit
and Beck (2013), this is the extent to which the findings of a study can be applied in other situations.
This enables a more inclusive and overall picture of the topic to be painted. The outcomes of the study
were checked to ensure that they will not be treated in isolation when used by other researchers. All
the processes within the investigation were reported in detail. This enables the works of future
researchers who may follow this paper’s process to be a prototype model. Additionally, all elements
of the process were covered in detail so that other researchers can understand the steps that have been
followed. Recruiting WCBA living in rural areas and those who spoke, wrote and understood Basic
English was designed to enhance transferability of findings to similar populations. However, limits to

113
transferability exist including the education and income level of patients, insurance coverage and
public health usage.
Main Study Findings
The responses from all 10 participants were analyzed using NViVo 11 qualitative analysis tool and
following the Colaizzi seven-step process. The themes generated were shortage of doctors and nurses,
distance to the hospital too far, inadequate money for transport to the hospital, long wait times to see
a doctor or nurse, poor patient outcomes, death of mother/child, paying for healthcare, inaccessibility
of healthcare staff, healthcare access during the last hospital visit, understanding of healthcare access,
understanding of impact of care on quality of life, physical environment of the hospital, unsatisfactory
patient care, shortage of medical equipment or supplies, shortage of healthcare providers, poor
communication by healthcare staff and unprofessionalism by healthcare providers.
The themes shortage of doctors or nurses, long wait times to see a doctor/nurse and inaccessibility
of
doctors or nurses were grouped together under “inadequate healthcare provider team” theme, which
was refined to “timeliness of care and patient Experience with Healthcare Providers,” to reflect a
healthcare quality metric. Shortage of medical equipment or supplies and unsanitary physical
environment were grouped together to form “unsatisfactory medical provision environment” theme,
which was refined to “patient safety” because it is a healthcare quality metric. The codes distance to
the hospital too far and inadequate money for transport to the hospital were grouped into a theme
named transport challenges. The code paying for healthcare was modified to inadequate healthcare
financing to form a theme. The codes poor communication skills, unsatisfactory patient care and
unprofessionalism by healthcare providers were grouped into one theme hostile hospital environment.
The code poor patient outcomes was defined into a theme “patient outcomes and safety” while the
code death of mother or child was defined as maternal and child mortality theme. Figure 7 below is a
word cloud of most frequently used words emerging from the interview responses.

114
Figure 7. Word cloud showing the frequency of the responses.
Table 1
Development of Codes into Themes and Subthemes
Codes
Themes
Subthemes
Long wait times to see a
doctor/nurse and
inaccessibility of doctors
or nurses.
Shortage of medical
equipment or supplies
and unsanitary physical
environment.
Distance to the hospital
too far and inadequate
money for transport to
the hospital.
Paying for healthcare.
Poor communication
skills, unsatisfactory
patient care and
unprofessionalism by
healthcare providers.
Patient outcomes and
death of mother or child.
Timeliness of Care and Patient
Experience with Healthcare
Providers.
Transport challenges
Inadequate healthcare financing
Hostile hospital environment
Patient Outcomes and Safety
Inadequate
healthcare provider
team.
Unsatisfactory
medical provision
environment.

115
Research Question 1: Perception of Process of Healthcare Access
Theme 1: Transport Challenges
Patients encountered transportation challenges when trying to get to the hospital. For example,
Martha
said that there was a day she was “feeling terrible with my pregnancy and had no means of
transportation to the hospital.” She had to endure the pain that day and “only went to hospital on my
scheduled day for antenatal visit.” Money to pay for transportation was often a challenge. Martha said
“It is hard for me personally because transportation to the hospital was usually very hard due to lack
of money.” Ongoing treatment procedures imply increased transportation costs. Megan said “For me
personally, it was hardship in the most part to afford transportation seek treatment.” Other patients live
too far from the hospital. Mary said “The distance to the hospital is far from my home and if I do not
have money for transportation, I will have to walk to the hospital which sometimes takes several hours
depending on my health condition.” Megan once missed an appointment due to transport challenges.
She said “I live far away from the hospital and sometimes difficult to find a vehicle to transport me to
the hospital.” Mercy added “…To find transportation to take you to the hospital is always a challenge
because I do not live close to the road.”
There are consequences when patients cannot access the hospital due to transport challenges.
According to Madelene, “Since there was no money to pay for transportation, I had to trek which is
quite a distance. By the time I got to the hospital, I was told that the doctor is not available and that I
should come back another day.” Mary had to self-medicate as she said “family member bought me
some medication from a local pharmacy which helped a little.” Melissa added “my child had very high
fever and I had no money to transport him to the hospital. However, I used cold water to reduce the
temperature.” Lastly, Miriam had no childcare for the other twin when one of them fell sick and

116
“…could not take him to the hospital because there was no one to stay home with the other child. I
used local treatment (herbs) by the help of a neighbor to stabilize him.”
Theme 2: Inadequate Healthcare Financing
Paying for healthcare is a limiting factor in accessing healthcare. Madelene said “Sometimes you are
required to do blood work which cost money and if you do not have the money, the treatment will be
incomplete.” Margaret added “It was hard for me due to economic hardship. I always struggled when
my child or myself fall sick to seek treatment. Struggled to raise money for transportation to the
hospital, consulting and buying medications.” Martha added “I often find it very difficult to gain
access to a doctor and sometimes unable to afford the medications prescribed.” All patients agreed that
lack of money affects their access to healthcare. Mary said that “If you do not have money, you will
not be treated…. If you are poor, the more you stay in line seeking treatment, the likelihood you may
not be seen by a nurse or a doctor.”
Patients self-medicated when they do not have money to go to a hospital. Maria said “My child got
very sick and I had no money to take him to the hospital. I bought medications from a roadside
pharmacy to manage the situation. Mercy added “Financial hardship is always the aspect that hinders
me sometimes for my child or myself to consult with a doctor. There were a few instances where I was
sick and treated myself both locally with herbs and also buying medications from a local pharmacy….
The system needs to change or else a lot of people will continue to die because of neglect. If you are
poor, you suffer the consequences.” Other consequences are death as Molly indicated “In order for the
doctor to attend to you, you have to have the full amount of money before they can attend to you even
in an emergency situation. If you do not have money, you can easily die because no one will even look
at you or attempt to treat you without money.” Theme 3: Hostile hospital environment.
All participants perceived the hospital environment to be hostile, and the patient care they received
was unsatisfactory in most cases. First, the healthcare providers had poor communication skills and
were rude, uncaring or shouted to patients. Mercy had never had a pleasant experience when consulting

117
with a nurse and gave an example of a humiliating situation she suffered under a nurse “In one of those
visits when I was pregnant, a nurse cursed me out when I was complaining of pain. She told me “did
I put the child in stomach?” Everyone in the waiting area at the lobby started laughing at me. It was
very humiliating and I will never forget that day.” She concluded that “nurses are not friendly and
have poor communication skills.” Later, she added that consulting with a nurse “…always cause me
more pain because of poor communication.” Madelene wondered whether healthcare providers are
paid well because “they often get angry when you consult and not very nice.” Later she added, “Most
staff will ignore you when you ask questions or seeking help.” Prompted for additional comments,
Margaret suggests customer service training for healthcare providers implying they may have poor
communication skills. She said “The doctors and nurses need more training on customer services. If
the Cameroon government can develop training programs to help them improve in their interactions
and relationship with patients, it will be very helpful.” Martha said “…the nurses are generally not
very caring and will shout at you when talking. I am familiar with it and so, not surprising to me.”
Later, she indicated that she has to “ignore their shouting to avoid further confrontation.” Miriam
added “Most nurses were very rude which I was not surprise. I was use to it because that is how they
have always been. The doctors on the other hand spend very little time to check my sick child despite
the very long wait time.” Miriam and Molly said that, some nurses were friendly and did their best to
take care of their children but others “were rude when communicating” while others “not so
concerned.”
Healthcare providers were also unprofessional in some cases and gave care to patients based on wealth
or social status. Maria said “I noticed that the doctors saw patients based on their economic and social
status. If you are rich and have influence in the society, you stand a better chance to be seen by the
doctor at all times and receive better care. If you are poor like me, you may not see the doctor at all.
The healthcare system works well for the rich than the poor.” Mary said although she had encountered
a few “nice” nurses, “…majority lacked good customer service…They see patients based on their

118
economic and social status. If you are wealthy and influential or your parents are influential in the
community, they will definitely get you in for check-up sooner.
They will also treat you nicely.” Later, she also said “If you are poor, the more you stay in line seeking
treatment the likelihood you may not be seen by a nurse or a doctor.” Madelene said that even when
the wait time is so long, “…often times people who came behind you will be called in first because
the nurse knows them.” Margaret added “Sometimes I feel like they do not care if your situation is
critical. They will consult with patients they know first or those who are wealthy.”
Besides treating patients based on class or influence, some healthcare providers treated patients in a
demeaning unprofessional manner. For example, Mary gave an example of something that happened
to her “…In one of my visits, a nurse wrote a prescription that was very expensive and when I tried to
question, she screamed at me and at the same time throwing my hospital book at me.” In other cases,
nurses were involved in selling medications meant to be given to patients. According to Miriam,
“…Some of them will focus more on trying to make extra money by selling their own medications.
Not sure where they get the medications from but
I was told by others that these are medications provided by some philanthropic organizations to help
patients.”
In some instances, patient care was unsatisfactory. Maria received poor care. She said “While at the
hospital, I did everything for myself despite my condition. When I called the nurse for help, she told
me she does not have time for that. I will got up and struggled by myself to get water to shower. The
nurses were not very friendly and nice.” According to Miriam, some nurses have been using one
syringe on more than one patient. She said “…I observed a nurse using one syringe (needle) on two
patients which was mind blowing. You have to be very vigilant when having an injection because a
nurse could use a used syringe on you causing other illnesses.” Madelene said “In the most part, the
nurses are very rude and do not seem to care about the patients. They will scream when
communicating. There was one occasion my child vomited while at the hospital and the nurse
screamed at me stating “You need to clean that mess immediately”. Later, she exemplifies this by

119
saying “when my baby need care after delivery, I will have to scream for help before someone will
come” and prompted for additional comments she added “most nurses and doctors are not very caring
by neglecting patients. They need to show love and compassion.” Maria added that “…the nurses came
across as not caring at all. I had some concerns with my baby and went to them several times to come
and check the baby but no one showed up until the following day. They are usually loud when they
communicate.” About her experience interacting with healthcare providers, she added, “The nurses do
not understand what a patient is going through. The way the nurse reacted when I arrived in the hospital
bleeding indicated to me, she had no idea what she was doing. I did not see the doctor until when I
was about to be discharged. Access to healthcare services needs serious improvement.” Mary gave
examples of when she received poor care. In one instance, “…I was told to wait in the sitting area. I
sat there for almost 2 hours and when I ask the nurse why it is taking so long, she got upset and told
me the doctor is not available and that I should go and come at another date. I finally saw the doctor a
month later.” In her most recent hospital visit when delivering her child, she said, “…it was a difficult
pregnancy and I was very sick. I was admitted in the hospital for 4 days without seeing the doctor….
I had no food for a while because the nurses would not even offer or ask if you are hungry.”
Research Question 2: Quality of Healthcare Services
Theme 4: Timeliness of Care and Patient Experience with Healthcare Providers
Patients have to wait longer before they can be seen by a doctor and sometimes, a nurse and this has
significant consequences on the quality of healthcare they receive. Megan said “The wait time at the
lobby was really disturbing to me considering my condition. It was very uncomfortable, and nurses
did not seem to understand how inconvenient and the pain I was going through.” Later, she added
“The wait time before finding a bed and finally seeing a doctor to begin treatment was very
disappointing. I was very sick and expected to have been placed on a bed sooner…. I felt the care was
not very good. I felt I was neglected for some time.” Melissa added “I went to the Mamfe general
hospital when I was sick with fever. It was a little frustrating for me because with my condition, it still

120
took the doctor very long to attend to me.” Miriam describes her last hospital visit “…I came in with
a lot of pain and sat at the waiting room for some time since there was a long line [of patients].”
Madelene added “The hospital is too small and lots of people waiting in line for treatment which takes
a while for a nurse to attend to you.” The long hours of waiting could be attributed to the shortage or
unavailability of healthcare providers. Most participants including Madelene, Maria, Melissa, Maria,
and Mercy agree that there is a shortage of doctors and nurses. According to Madelene this “…made
it difficult to receive care when you need it in a timely manner.” The few doctors available are too
busy to see patients and delegate the duty to nurses, who are also overwhelmed or see patients for an
inadequate amount of time.
Madelene exemplifies this situation “I consulted with a nurse for all my visits. There was one time I
requested to see a doctor and I was told the doctor is over booked already. I was also told by the nurse
that my condition is not such that requires to see a doctor.” Margaret consulted with a doctor only
when there was a complication. She said “I consult with a doctor only with complications such as
having a C-section when my child was bridged.” Maria added “I saw a nurse when I arrived at the
hospital and that is the only nurse I saw until I left. I was told that the doctor only sees patients in an
emergency situation.” Nurses may prescribe medication when doctors are not available as Mary
illustrates “The doctor was not available on all three occasions I went to the hospital… the nurses
could not really help me because they confessed, they do not have the expertise to take care of my
sickness. However, medications were written to be filled at a local pharmacy.” Unavailability of
doctors has consequences for healthcare delivery as Meghan illustrated “When I was rushed into the
hospital, I was in pain and exhausted. I sat in the hospital lobby for sometime because the doctor was
not available and the nurse did not know what to do.”
Sometimes both nurses and doctors were not available, postponing healthcare access as Melissa
showed

121
“…when I went to the hospital to consult and there was no doctor or nurse to attend to me and I had
to go back home and returned to the hospital the following day.” Later, she added “The fact that it is
always difficult to see a doctor is troubling to me especially if you have a condition requiring a doctor’s
professional advice.” Mercy said there was only one doctor and “…it is difficult to consult with a
doctor... Unfortunately, if you are poor you may never seen a doctor.”
Untimely care and poor patient experience with accessing healthcare particularly due to
inaccessibility and shortage of doctors and healthcare providers influenced the perceived quality of
healthcare negatively.
Theme 5: Patient Safety
The shortage of medical equipment or supplies and unsanitary physical environment compromised
patient safety. The study participants complained of a shortage in medical supplies. Martha, Mary,
Madelene and Meghan all confessed that the hospital they visited lacked adequate medical supplies.
Mary said, “The lack of equipment and basic medical supplies is a huge problem needing attention.”
In instances of shortage, patients may be asked to purchase them as Mary said “…basic items such as
wound dressings, syringes, bandages etc. are not available. They will tell you to go get these items
before they can treat you. There was a lot of concern about nurses using one syringe for multiple
patients.”
In addition, the participants complained about unsanitary physical conditions in the hospital. Mary,
Molly, Melissa, and Madelene all described the hospital as being “unsanitary.” Mary said “…the
hospital environment is not clean enough and needs improvement” while Melissa added “the sanitary
condition definitely needs improvement as you could smell bad odor” and the infrastructure is in “bad
shape.” Miriam added that although the nurses took care of her child, she was not “…very comfortable
with the hospital environment. The hospital was not that clean and had a terrible smell.” In addition,
lighting is a problem as Molly said “Sometimes there are no lights and we have stay in the dark. The

122
generator they have is not very effective.” Unsanitary conditions in the hospital and shortage of
medical supplies may compromise patient safety and thus, influence the quality of healthcare.
Research Question 3: Understanding the Impact of Healthcare Services
The participants seemed to understand the impact of healthcare services as shown in Figure 5. The
following themes emerged from the discussion:
Theme 6: Impact on Patient Outcomes and Safety
Melissa observed that the rudeness and negligence exhibited by nurses may “slow down the healing
process.” She shares how poor patient care impacted her health and led to negative outcomes “…the
medication prescribed for infection did not work at all. Had a doctor seen me, the outcome of my
illness would have been entirely different. I suffered a great deal of pain for the next several days
before I was able to resolve the infection problem with a new medication.” Margaret understood the
impact of healthcare services on patient outcomes and safety. She outlined the importance of maternal
and child care by saying that if “… mother and child are not consulting with a doctor or nurse when
they are sick and if the doctor/nurse do not attend to them soon enough when they are sick, it may lead
to worsening of the condition and ultimately death. Margaret also gave an example of a case where a
lack of immediate attention by the healthcare staff threatened her child’s health. She said, “…In 2017
I took my daughter to the hospital when she had high fever and there was doctor/nurse to attend to her
for several hours. The wait time led to her having a convulsion.” Meghan said “Every human being
deserves basic healthcare services. Specifically, if women and children are unable to gain access to
this basic healthcare services, it could aggravate their current condition leading to complications and
possible death.” Molly summarized this by stating that “Good health requires…being able to go to the
hospital to seek treatment when you are sick. If you cannot take care of your baby and yourself, the

123
situation gets worse and could cause life. Limited finances to provide for their medical care.” The
patients understood the impact of healthcare services on their health outcomes and safety.
The patients explained the impact healthcare services had on maternal and child mortality. Madelene
understood that poor case can cause loss of lives. She defined poor care as “…a doctor or a nurse not
taking time to check the baby or the mother to figure out what their conditions are.” She added that
“The shortage of doctors and nurses and lack of money for hospital visits could worsen a health
situation and ultimately causing lives.” Maria also said her life was at threat at one point due to
negligence. She said “…I was bleeding and the nurse that received me showed no sympathy and did
nothing for several hours. I thought I was going to die.” Martha acknowledged that failure to attend
hospital when she is sick can harm her health. She said “With the economic hardship making it difficult
to go to the hospital when needed could really cause a major health problem down the road.” She gave
an example of when she missed an appointment due to lack of money for transport “…it could have
aggravated my sickness if not of the traditional medication. Therefore, without basic healthcare
services, it could worsen health condition leading to death.” Mary added “The fact that there is lack
of basic items to care for patients, using one syringe for more than one patient and dirty environment
could impact quality of care. It could cause the death of a child or a mother.” Meghan witnessed an
unfortunate case of death due to poor healthcare access. She said, “I have observed in some occasions
where a pregnant woman died with a baby in her tommy because she did not have money for C-section
and the doctor refused to treat her.”
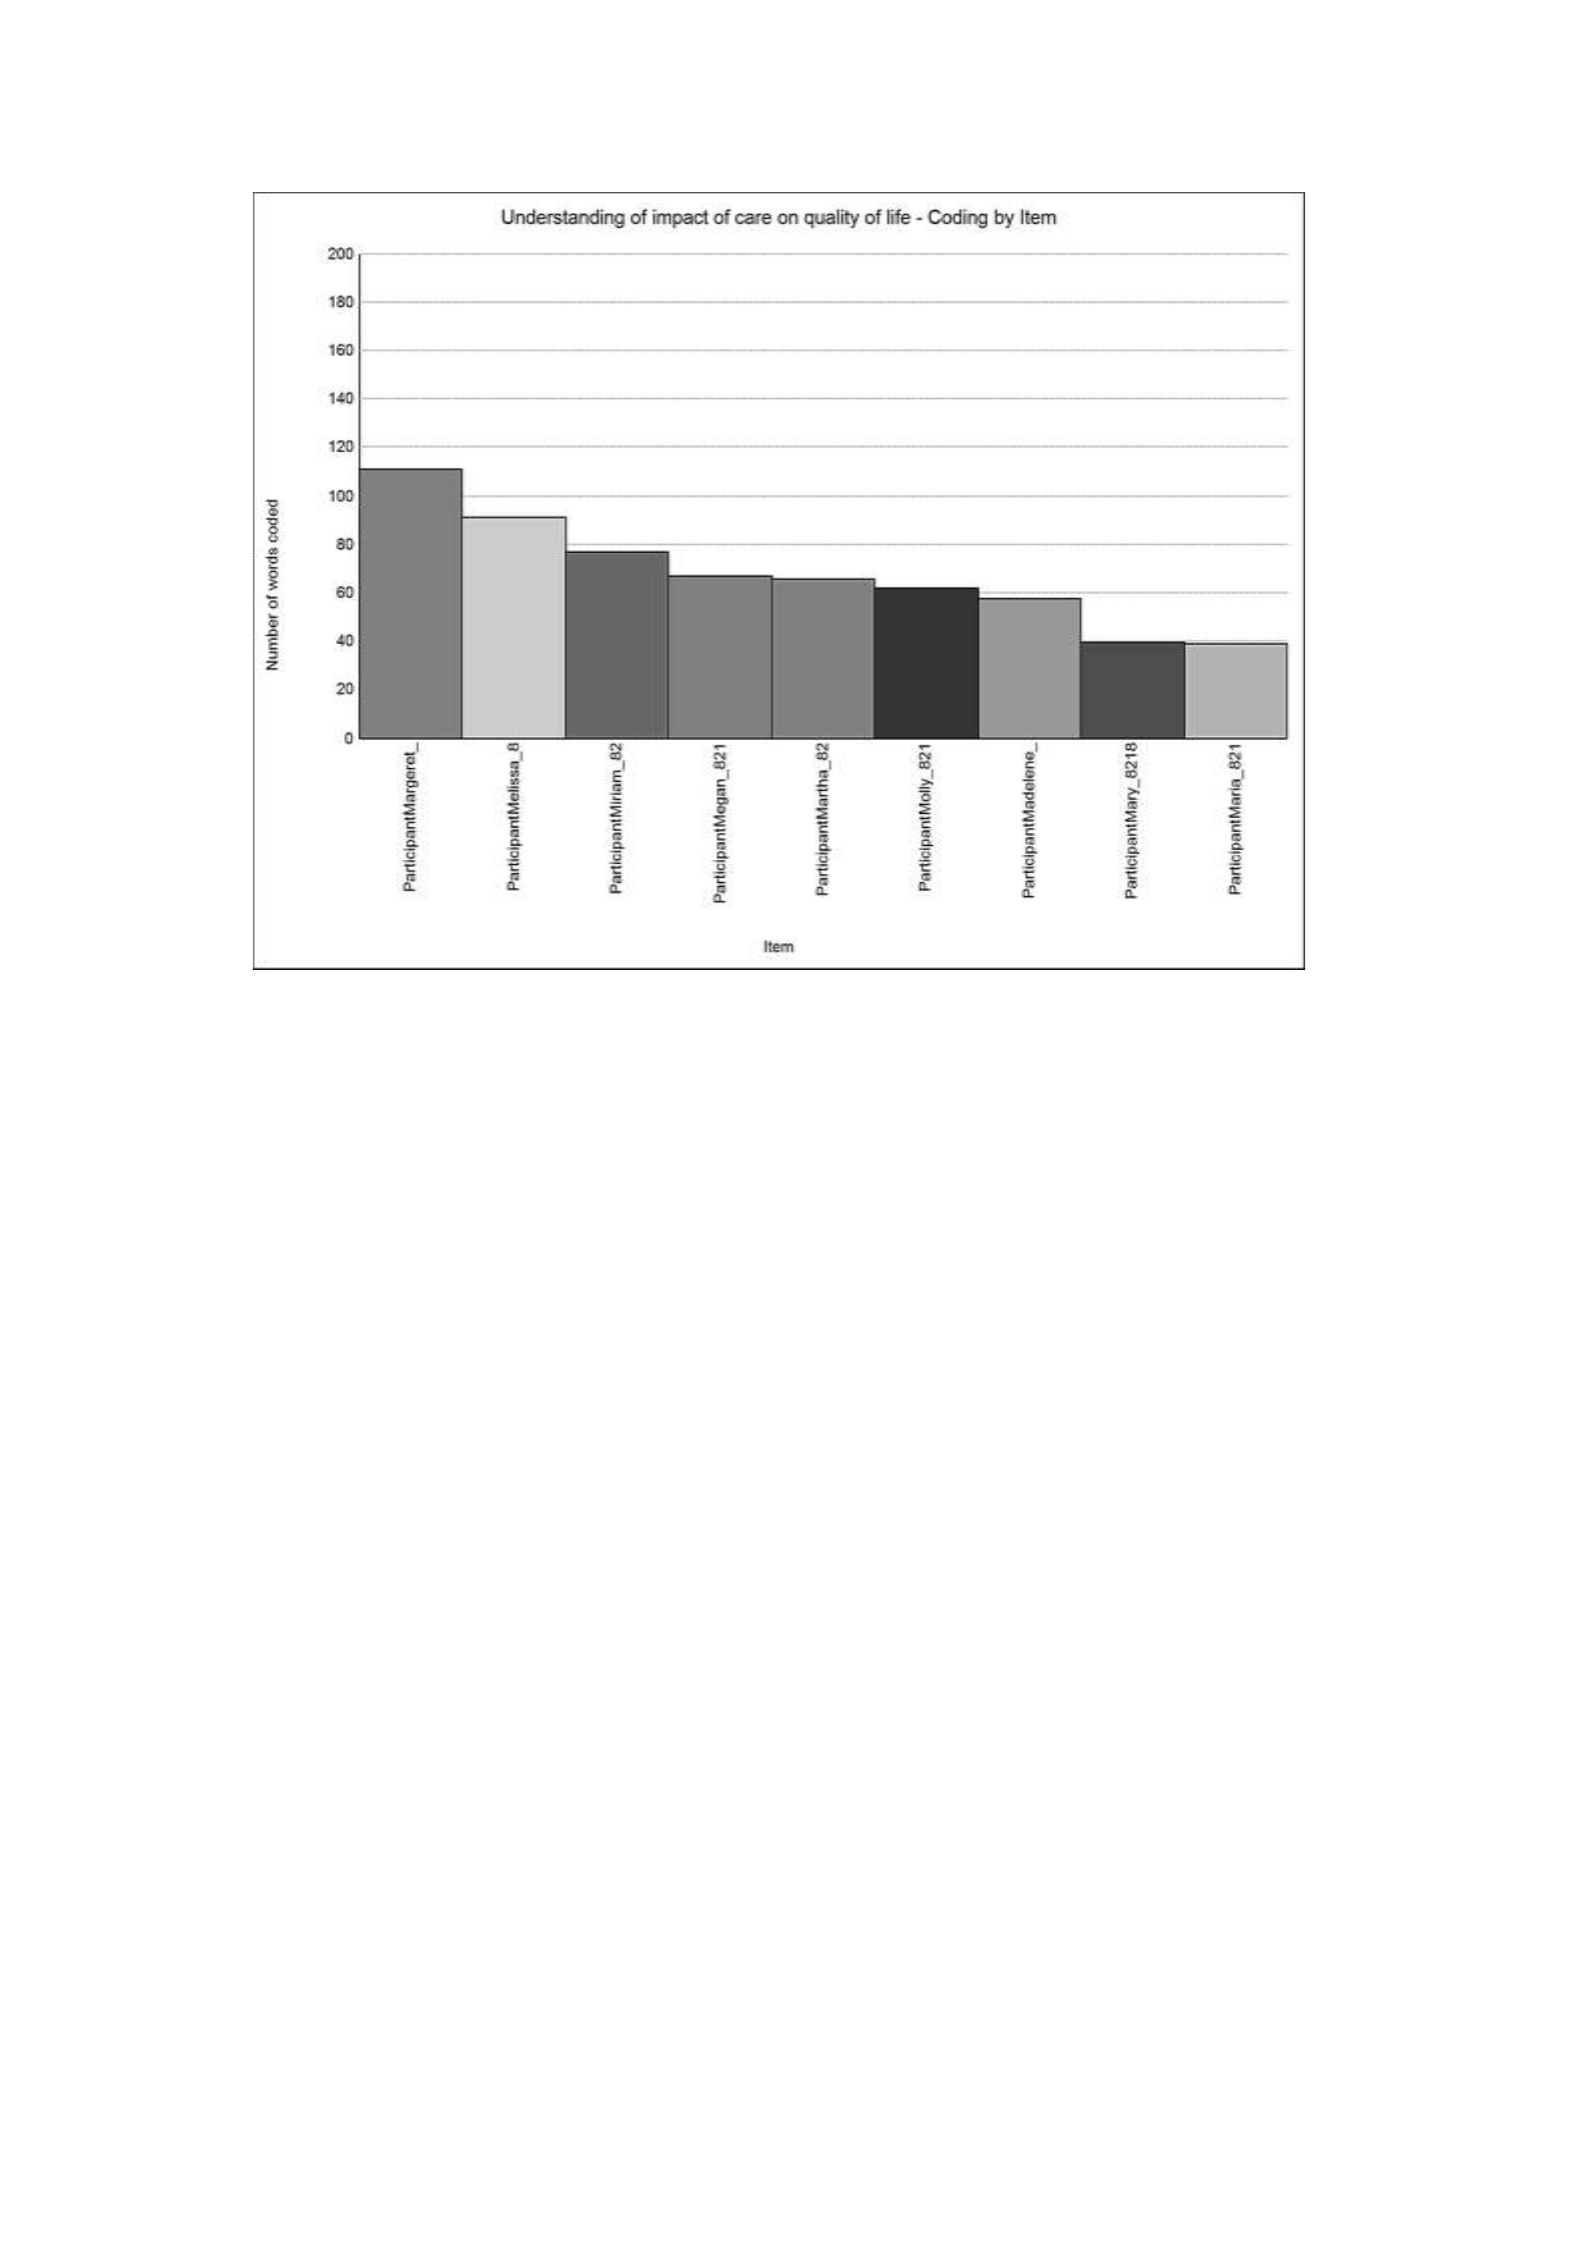
124
Figure 8. Understanding the impact of healthcare number of words coded per participant.
Summary
The interview with participants revealed that they understood access to healthcare, at least in terms
of
maternal and child care. They knew of the impacts of healthcare access on quality of life and knew
what they wanted from a healthcare provider. The participants perceived the healthcare they received
as poor and of substandard quality and highlighted ways that the healthcare failed to meet their needs
or expectations. They talked about the poor communication skills exhibited by their healthcare
providers including being rude, negligent and unprofessional, the unsanitary conditions of the hospital
and the shortage of supplies. In addition, they discussed the factors that made access to healthcare a
challenge. These factors include transportation and a shortage of healthcare providers. NViVo 11
qualitative analysis tool was used to analyze the responses of the participants. The emerging themes
were transport challenges, paying for healthcare, hostile hospital environment, timeliness of care and
patient experience with healthcare providers, patient safety, the impact of healthcare access on patient
outcomes and safety and impact of healthcare access on maternal and child mortality. The themes are

125
interpreted and discussed further in the following chapter. Chapter 5 will introduce a brief overview
of the seven themes identified in the previous chapter, an interpretation of findings, limitations of the
study, recommendations, implications for social change, and a conclusion.
Chapter 5: Discussion, Conclusion, and Recommendations
Introduction
The data analysis in Chapter 4 yielded six themes: transport challenges, paying for healthcare, hostile
hospital environment, timeliness of care and patient experience with healthcare providers, patient
safety, and the impact of healthcare access on patient outcomes and safety. These themes reflected
WCBAs’ perspectives about healthcare access in Cameroon, the quality of healthcare access, and their
understanding of the impact of healthcare access on quality of life. In this chapter, these findings are
interpreted and discussed by themselves and in the context of the literature. In addition,
recommendations are suggested, implications of the findings are discussed, and limitations of the study
are outlined.
Interpretation of Findings
The findings showed that transport challenges hindered access to healthcare due to several reasons
such

126
as lack of money and distance from the hospital. Some patients tried to walk in order to receive medical
care, but often, they were too weak. The consequences were delayed access to care when they arrived
too late to find out the doctor was gone for the day as well as postponement and missed appointments.
Some patients selfmedicated when they could not access the hospital, and others turned to traditional
medicine. For example, Martha had to endure pain despite being pregnant because she could not
afford to pay for transportation and waited until her scheduled antenatal visit to have a checkup. Others
like Melissa turned to options like pouring cold water on her child to reduce fever. All of these
consequences posed risks for mothers and children during pregnancy and the postpartum period.
Living in rural and/or remote areas further compounded the problem of poverty and difficulties in
accessing public healthcare services. The literature review highlighted some problems of healthcare
access for rural populations including distant health facilities, lack of means to reach hospitals, poor
knowledge of public health, and lack of funds to settle medical bills. The findings of this study
particularly acknowledge the long distance to hospitals and lack of money to pay for transportation to
reach hospitals.
Paying for healthcare is a major hurdle in terms of access to healthcare. Some patients had
public
insurance while others lacked insurance altogether. Out-of-pocket costs for healthcare were a major
challenge to all participants, since almost all identified as coming from low-income households. They
had to pay money to get transportation to the hospital, consult with doctors, and buy medications. The
participants were aware that they could not be treated if they did not not have money. For example,
Molly explained how one must have the full amount of money to get attended by a doctor, even in an
emergency situation. The situation is dire, according to Molly, because regardless of the patient’s
situation, treatment cannot be initiated unless the patient pays first. Ajong et al. (2016) reported a 25%
to 19% decrease in childbirth with medical practitioners between 1993 and 2003 as well as delayed
prenatal care in at least 45% of women. Although there are many factors that may be attributed to the
decrease in the number of practitioner-attended births, the costs of these services are an important

127
factor. The findings of the qualitative analysis also revealed that equity is a significant problem, as
money determined who gets access to healthcare services, including doctors and whose treatment gets
prioritized. In the literature review, factors that affected equitable healthcare access such as race,
ethnicity, religion, and gender were discussed, but social status and financial ability were not, because
often public health is meant to be accessible to all. However, among the participants, this was not
usually the case. Some participants were not insured and those who were received a public insurance
program. The Cameroonian government allocated only 6% of its budget on healthcare (Abrokwah et
al., 2016), and thus, it is possible that public health is significantly underfunded and patients have to
still pay for services out-of-pocket. In a country where 33% of the population lives below $1.25 a day
(World Bank, 2011), out-of-pocket payments for healthcare and mandatory payment before receiving
healthcare can be a significant hindrance to healthcare access.
From the data, it was also obvious that the hospital environment was not friendly to patients and
often
they had to endure just to get treatment. The patients complained of poor communication skills of
healthcare providers such as that nurses were rude, shouting at and humiliating participants in front of
other patients. The nurses were usually unprovoked, such as in the case of Mercy, who wanted to
notify the nurse about the pain she was having when the nurse humiliated her in the hospital lobby, as
well as Martha, who learned to cope with the nurses’ rudeness and shouting to get treatment, and Mary,
who had a book thrown at her for asking why her prescription was expensive. The participants also
highlighted unprofessionalism from healthcare providers who treated or prioritized some patients
based on their wealth or influence in the community. In a setting with limited doctors, patients who
had to see a doctor were likely to be affluent or influential in the community at the expense of clinically
serious cases. Patient care was unsatisfactory at times, and patients were forced to take care of
themselves. For example, Maria said she would get water for the shower by herself because the nurse
said she did not have the time to do so. Miriam explained how one had to be vigilant to ensure they
get the right treatment. Mary explained how she went without food while being admitted. These

128
findings were consistent with those discussed in the literature review who reported scolding of women,
verbal abuse, negative personnel attitudes, and slapping of women during labor and delivery.
Considering the nursepatient ratio of 1.6 nurses for 1000 people (World Bank, 2011) and even more
serious discrepancies of nursepatient ratios in rural areas (CDBPH, 2012), it may be that nurses are
overworked and amidst all other challenges of the Cameroonian healthcare system, they have to do an
almost impossible task. Overworking may also result in burnout syndrome, particularly where the
nurses are not adequately supported and their mental health is not prioritized within employment
contexts. Occupational stress has an impact on nurses’ caring behaviors (Sarafis et al., 2016).
All participants perceived the quality of care they received as being low. Using three patient care
metrics, timeliness of care, patient experience, and patient safety, the findings revealed that the quality
of care is not satisfactory. First, healthcare was not timely. Patients had to wait long times to get access
to healthcare providers. Patients also had to wait for long times at the lobby despite their condition.
Meghan said that, she had to wait for a long period despite the fact that she was in pain and no nurse
seemed to bother. Triage sorts out patients according to urgency or emergency, resulting in better
patient flow, reduced wait time, and better patient satisfaction (Jarvis, 2016). However, it is not clear
the extent to which such and other measures are taken to improve the overall patient experience and
hospital efficiency in the setting where the study was conducted.
The long wait times are sometimes caused by many patients and inadequate human resources. The
patients often have to consult with nurses, who are also involved in treatment and prescribing because
doctors are unavailable or inaccessible. Where doctors are available, they may be too few to see all
patients, and when they do, they do not have adequate time and hence conduct a short patient
assessment as some patients said that the doctors only spend a few minutes with them. The literature
review highlighted some of these challenges with healthcare providers particularly the shortage of
doctors and nurses. The doctor to patient ratio in Cameroon is two doctors per 10,000 people, well
below the recommended minimum of 23 for every 10,000 people (Poverty and Health, 2013). Rural

129
areas such as the setting of the present study are likely to have even fewer doctors. With fewer
healthcare providers, the queues and wait times are long, and the few available doctors cannot attend
to all patients. When they attend to patients, they are allowed a few minutes for each, such that the
patient feels like they did not get adequate time with the doctor. The length of time a doctor spends
with the patient is often used by patients to judge the satisfaction they can attach to their healthcare
service (Surbakti & Sari, 2018). A short patient-doctor experience may contribute to patient
dissatisfaction with their care. When the patient’s condition is out of scope for the nurse, the patient
has to wait until the doctor is available despite their health condition or emergency. For example,
Meghan explained how she had to wait in the lobby for a doctor because the nurse did not know what
to do.
The findings also point to shortages of medical supplies and an unsanitary hospital
environment
which put patient safety at risk. All participants acknowledged that the hospital they visited lacked
adequate medical supplies. In some instances, patients were asked to purchase these supplies before
they could receive treatment. Such supplies include syringes, wound dressings and bandages. This is
an additional financial burden to patients who are barely able to pay for healthcare. In addition, there
is a patient safety risk in case some supplies such as syringes are used on multiple patients as Mary
said that she had observed this happen. Besides the shortage of supplies, the participants described the
hospital as being unsanitary, smelly and dirty. In other cases, there were problems with lighting and
patients had to stay in the dark. All of these factors can compromise patient safety and thus, influence
the quality of care that patients receive. Shortage of medical supplies can be directly attributed to
healthcare funding challenges. In the literature review, insufficient government expenditure was
explained as the root cause for a shortage of essential materials such as equipment, beds, and drugs.
The 27% healthcare burden that the government finances (World Bank, 2013) may not be adequate
even when patients have to pay.

130
The findings revealed that the participants understood the impact of healthcare services on their
lives. They talked about how poor healthcare could lead to death or adverse effects. Thus, two themes
were created; impact on patient outcomes and safety and impact on maternal and child mortality. On
the impact of patient outcomes and safety, some participants noted that the quality of healthcare they
received impacted their healing process. Melissa said that the negligence that nurses exhibited might
impact the healing process. The nurses also prescribed medicine which according to her did not work
and had to endure pain for several days before she got new medication. Nurses’ roles are not to
prescribe medication, and there are consequences when healthcare providers do not play their roles as
should be. Long wait times at the hospital also impacted patient outcomes and safety for Margaret
whose child convulsed when she stayed too long at the hospital lobby without attention. Triage is
supposed to deal with some of these issues by prioritizing patient care according to urgency. However,
this does not seem to occur and patients’ outcomes, safety, and lives are at risk.
The participants also understood that healthcare access had an impact on maternal and child
mortality. Most participants feared that the negligence at the hospital was a threat to all their lives. For
example, Maria talks of how she as bleeding and the nurse were not concerned for at least several
hours. She said she was scared she was going to die. Martha also acknowledges how the lack of basic
healthcare can lead to worsening of sicknesses leading to death. Mary said that the sharing of syringes
that she observed in addition to the unsanitary conditions in the hospital could cause maternal or child
mortality. Meghan recalls when a pregnant mother died because she could not afford money for a C-
section. All of these instances show that these participants are well aware of the impact that healthcare
access has on their health and life.
The above findings are in agreement with those reported in previous research. Women, especially
from
low-income households, still have to use public health services regardless of their perceptions due to
lack of alternatives. These sentiments are shared by Fotso and Mukiira (2011). Consistent with Odetola
(2015), economic and health-system factors such as quality of care, scarcity of healthcare facilities

131
and personnel and demographic variables like educational level and income influence patients’
perceptions. However, it is not completely accurate what Soh (2013) said that the WCBA in Cameroon
fail to access healthcare because they do not recognize it as a fundamental health right. They perceive
healthcare access as important for themselves and their children and whatever factors that delay
healthcare access are often beyond their control. Factors such as finances, transport challenges, a
hostile hospital environment where healthcare providers are often rude and unprofessional, long wait
times and unavailability of healthcare personnel, shortage of supplies and unsanitary hospital space
all contribute to the extent that WCBA access healthcare and the quality of healthcare they can get.
Thus, the problem of healthcare access is more systemic and institutional than it is patient-focused.
Also, religious and sociocultural practices did not influence healthcare access as reported by CDBPH
(2011). At the end of the day, all the women interviewed wanted quality healthcare despite their
sociocultural or religious
beliefs.
Theoretical Lens
The utilization model developed by Adey and Anderson in the 1960s was utilized to facilitate
understanding of access to healthcare. The examination of the lived experiences of WCBA using the
healthcareutilization model provided a clearer view of women’s access to healthcare in Cameroon.
This model helped facilitate a comprehensive understanding of the reasons for poor access of
Cameroon women to healthcare services.
Study findings revealed the existence of several impediments in the process of access to healthcare
by
the study population. These were attributed by a number of factors to include; inadequate healthcare
provider team (doctors and nurses), transportation challenges, inadequate healthcare financing, and
shortage of medical equipment and supplies. The findings also showed that WCBA in seeking access
to healthcare not only encountered these challenges but were aware of the effects of healthcare on their
outcomes and safety as well as maternal and child mortality. The conceptualization of the healthcare

132
utilization model covered all aspects of this study. There are systemic challenges that affected
healthcare access and these need to be adequately addressed to reduce maternal and child mortality
among women of child-bearing age.
Limitations of Study
The sample size (10 participants) may have been too small or homogeneous to make accurate
generalizations. For example, the literature review showed that religious beliefs, sociocultural values,
and perceptions of WCBA might influence access to healthcare. However, this was not the case with
the study participants, which may be because the sample was not heterogeneous enough. Time,
resources and personal bias were also a major limitation. The process of analyzing and making sense
of the data was a time-consuming exercise. My prior knowledge of the health care challenges of this
population (WCBA) presented some degree of bias. This was minimize using a reflexivity strategy to
ensure my preexisting knowledge of the study did not influence the research process.
Recommendations
Regular training of nurses and doctors can equip them with communication skills to enable
them to communicate with patients more effectively. Motivation and discipline by the hospital
management can also help inspire accountability and can contribute to better patient care. The second
set of recommendations are systemic and aim to address systemic issues that plague the healthcare
system in Cameroon and which have a direct impact on maternal and child care. Higher budgetary
allocations and more collaborations between the private and public sector as well as the donor
community can help increase funding and boost healthcare resources. In addition, I recommend the
utilization of community nursing programs where healthcare practitioners travel to communities at
least to conduct check-ups and alleviate the need for patients to travel long distances to get to hospitals.
In addition, incorporating traditional medicine into healthcare particularly in rural areas can help. This
would be done through training traditional birth attendants to conduct uncomplicated births in rural
areas. A systematic review by Byrne and Morgan (2011) showed that traditional birth attendants could

133
be integrated with formal health systems successfully to increase skilled birth attendants. The WHO
(2015) suggested the incorporation of traditional birth attendants into formal healthcare after further
research.
Traditional medicine has been explored as a complement to western medicine style, and certain aspects
of traditional medicine can be investigated further for use by women in rural areas and who cannot get
to hospitals in time. The participants in the study already admitted to using traditional medicine when
they could not access healthcare. Further research is required to assess how traditional medicine can
be incorporated into current practice. Lastly, motorcycles common in many rural areas in African
including Cameroon can be modified to provide “ambulatory” transport to hospitals during
emergencies particularly in areas with limited access. They have been implemented in villages in
certain areas in Uganda, Kenya and Malawi. Hofman, Dzimadzi, Lungu, and Ratsma (2008) reported
that motorcycle ambulances in Malawi were useful and affordable means of referral for emergency
obstetric care.
Implications for Social Change
The present study has shown that women know and understand the importance and impact of
healthcare access not only on the quality of life but also on the lives, health, and safety of themselves
and their children. They have borne the pain of an underfunded healthcare system with significant
challenges such as shortage of supplies, unsanitary conditions, poor attitudes from healthcare
practitioners and a shortage of healthcare providers. Most of the time they cannot afford to pay for
healthcare services, transport and even when they do, they are frustrated that they still cannot get to
consult with a doctor and sometimes are not treated so nicely.
The study has shown that there is a big problem with healthcare facilities as well as systematic
problems
with the healthcare system. All is not lost because there is so much that can be done to help these
women and children particularly those living in rural and/or remote areas. Adopting practices,

134
infrastructure, and mechanisms that are adaptable to these regions as suggested above can help address
some of these challenges.
For social change, the findings of the present study show that the biggest problem is not with the
patients (women of child-bearing age), but with the healthcare system. Thus, attempts to improve
maternal and child care, can be solely targeted at making public health more accessible and
accommodating to these women and not changing their perceptions.
Conclusion
The purpose of this qualitative study was to examine how WCBAs seeking healthcare services
perceive
healthcare access through their lived experiences and access the existing healthcare system in
Cameroon. The study aimed to answer three research questions. The first research question was: how
do WCBA seeking maternal/child healthcare services in Cameroon perceive the process of healthcare
access through health institutions? The findings of the study showed that WCBA perceived the process
of seeking maternal/child healthcare as a difficult one characterized by challenges in getting transport
to medical facilities because they cannot afford it or live too far from the hospital, challenges in paying
for healthcare because they pay out-ofpocket, come from low-income households and most are
unemployed or employed only part-time and without much social support. They also have to withstand
a hostile hospital environment as characterized by poor communication skills and unprofessionalism
of the nurses. The patients often had to endure insults, negligence, and humiliation from the healthcare
providers and do not always get access to doctors. However, they persevere for lack of alternatives.
The second research question was: how do WCBA seeking maternal/child healthcare services
in Cameroon perceive the quality of healthcare services offered through healthcare institutions? The
study found out that WCBA seeking maternal/child care have to deal with shortages of medical
supplies and healthcare providers and unsanitary conditions, which influence timeliness of care,

135
patient experience, and patient safety negatively. Thus, the participants perceived the healthcare they
receive as being of poor quality but still have to use it because private care is out of their reach.
The third question was: how do WCBA seeking maternal/child healthcare services in Cameroon
understand the impact of healthcare services on their quality of life? The study found out that WCBA
seeking maternal/child healthcare services understood the impact of healthcare services on the quality
of life. They were aware of the effects of healthcare on their outcomes and safety as well as maternal
and child mortality. Some had observed and experienced maternal, and child mortality due to
negligence at the hospital and they are constantly afraid that they are not safe. In conclusion, there are
systemic challenges that affected healthcare access and these need to be adequately addressed to
reduce maternal and child mortality among women of child-bearing age.

136
References
Abrokwah, S. O., Moser, C. M., & Norton, E. (2016). The impact of social health insurance on
household
fertility decisions. Journal of African Economies, 25, 699-717. doi:10.1093/jae/ejw013
Aday, L. A., & Andersen, R. (1974). A framework for the study of access to medical care. Health
Services
Research, 9(3), 208.
Andersen, R. M. (1968). A behavioral model of families’ use of health services. Retrieved from
https://ssa.uchicago.edu/sites/default/files/uploads/RS25.
Ajaegbu, O. O. (2013). Perceived challenges of using maternal healthcare services in Nigeria. Arts
and Social
Sciences Journal, 4. Retrieved from http://astonjournals
.com/manuscripts/Vol2013/ASSJ-65_Vol2013.pdf
Ajong, A. B., Njotang, P. N., Kenfack, B., Yakum, M. N., & Mbu, E. R. (2016). Knowledge of women
in
family planning and future desire to use contraception: A cross sectional survey in urban
Cameroon.
Retrieved from https://bmcresnotes.biomedcentral.com/articles/10.1186/s13104-016-2155-7
Ako, S., Fokoua, S., Sinou, M., & Leke, R. (2015). Reproductive health in Cameroon. Retrieved from
http://www.gfmer.ch/Endo/Reprod_health/Cameroon/Net
_Reproduction_Cameroun.htm

137
Al-Busaidi, Z. Q. (2008). Qualitative research and its uses in health care. Sultan Qaboos University
Medical
Journal, 8(1), 11.
Bakeera, S. K., Wamala, S. P., Galea, S., Peterson, S., & Pariyo, G. W. (2009). Community perceptions
and
factors influencing utilization of health services in Uganda. International Journal for Equity
in Health,
8, 25. doi:10.1186/1475-9276-8-25
Braveman, P. (2014). What are health disparities and health equity? We need to be clear. Public Health
Reports,
129, 5-8. doi:10.1177/00333549141291S203
Braveman, P., & Gruskin, S. (2003). Defining equity in health. Journal of Epidemiology and
Community
Health, 57, 254-258. doi:10.1136/jech.57.4.254
Braveman, P. A., Kumanyika, S., Fielding, J., LaVeist, T., Borrell, L. N., Manderscheid,
R., & Troutman, A. (2011). Health disparities and health equity: the issue is justice. American
Journal of Public Health, 101(S1), S149-S155.
Byrne, A., & Morgan, A. (2011). How the integration of traditional birth attendants with formal health
systems
can increase skilled birth attendance. International Journal of Gynecology & Obstetrics,
115(2), 127-
134.
Center for Development of Best Practices in Health (CDBPH). (2012). Optimizing the
use of antenatal care services in Cameroon. Retrieved from
http://www.who.int/evidence/sure/FRPBCPNEN.pdf
Center for Reproductive Rights. (2003). Cameroon. Retrieved from http://www
.reproductiverights.org/sites/default/files/documents/cameroon.pdf

138
Chandra-Mouli, V., Camacho, A. V., & Michaud, P. A. (2013). WHO guidelines on preventing early
pregnancy and poor reproductive outcomes among adolescents in developing countries.
Journal of Adolescent Health, 52, 517–522. doi:10.1016/j
.jadohelth.2013.03.002
Chauvin, P., & Simonnot, N. (2012). Access to health care for vulnerable groups in the European
Union in
2012. Retrieved from http://www.europarl.europa.eu
/document/activities/cont/201302/20130208ATT60776/20130208ATT60776EN
.pdf
Chenail, R. J. (2011). Interviewing the investigator: Strategies for addressing instrumentation and
researcher
bias concerns in qualitative research. The Qualitative Report, 16(1), 255-262. Retrieved from
http://nsuworks.nova.edu/cgi/viewcontent.cgi?article=1051&context=tqr.
Chi, P. C., Urdal, H., Umeora, O. U., Sundby, J., Spiegel, P., & Devane, D. (2015). Improving
maternal, newborn and women’s reproductive health in crisis settings. The Cochrane
Database of Systematic Library, 8(8), 1–26. doi:10.1002/14651858
.CD011829
Cleary, M., Horsfall, J., & Hayter, M. (2014). Data collection and sampling in qualitative research:
does size
matter?. Journal of advanced nursing, 70(3), 473-475.
Commeyras, C., Ndo, J. R., Merabet, O., Koné, H., & Rakotondrabé, F. P. (2004). (Study of access to
health care and drugs in Cameroon: 1. Methods and validation). Sante (Montrouge, France),
15(3), 161–166.
Creswell, J. W. (2013). Research design: Qualitative, quantitative, and mixed methods approaches.
Thousand
Oaks, CA: SAGE Publications.

139
Deaton, A., & Tortora, R. (2015). People in Sub-Saharan African rate their health and health care
among the lowest in the world. Human Affairs, 34(3), 519–527. doi:10.1377/hlthaff.2014.0798
Djomo, J. M. N., & Sikod, F. (2012). Multidimensional analysis for agricultural producers’ health care
in
Cameroon. International Journal of Economics and Finance, 4(5), 124–135.
doi:10.5539/ijef.v4n5p124
Edie, G. E. H. E., Obinchemti, T. E., Tamufor, E. N., Njie, M. M., Njamen, T. N., & Achidi, E. A.
(2015). Perceptions of antenatal care services by pregnant women attending government
health centers in the Buea Health District, Cameroon: A cross sectional study. Pan African
Medical Journal, 21(1).
doi:10.11604/pamj
.2015.21.45.4858 Egbe,
M. E. (2014). Country
report: Healthcare system
of Cameroon: Socio-
economic characteristics;
historical
context; organizational & financial aspects; major public health programs & challenges;
strength and weaknesses. Retrieved from https://
www.researchgate.net/publication/236166490_COUNTRY_REPORT_The
_Healthcare_System_of_Cameroon_Socio-Economic_Characteristics_Historical
_Context_organizational_Financial_Aspects_Major_Public_Health_Programs
_Challenges_Strength_and_Weaknesses
Eide, A. H., Mannan, H., Khogali, M., van Rooy, G., Swartz, L., Munthali, A. & Dyrstad, K. (2015).
Perceived

140
barriers for accessing health services among individuals with disability in four African
countries. PloS One,10, 761–775. doi:10.1371/journal
.pone.0125915
Erickson, F. (2012). Qualitative research methods for science education. In B. J. Fraser, K. Tobin, &
C. J.
McRobbie (Eds.), Second international handbook of science education (pp. 1451–1469).
Dordrecht, The
Netherlands: Springer. doi:10.1007
/978-1-4020-9041-7_93
Fletcher, T. R., Clements, A. D., & Bailey, B. (2016). Identifying intimate partner violence during
pregnancy in
prenatal care settings. International journal of health sciences education, 3(1), 3.
Fotso, J. C., & Mukiira, C. (2011). Perceived quality of and access to care among poor urban women
in Kenya
and their utilization of delivery care: Harnessing the potential of private clinics? Health
Policy and Planning, 27, 505–515. doi:10 .1093/heapol/czr074
Gulliford, M., Figueroa-Munoz, J., Morgan, M., Hughes, D., Gibson, B., Beech, R., & Hudson, M.
(2002).
What does “access to health care” mean? Journal of Health Services Research & Policy, 7,
186–188.
doi:10.1258/135581902760082517
Gulliford, M., & Morgan, M. (Eds.). (2003). Access to health care. New York, NY: Routledge.
Harper, M., & Cole, P. (2012). Member Checking: Can Benefits Be Gained Similar to
Group Therapy?.The Qualitative Report,17(2), 510-517. Retrieved
From http://nsuworks.nova.edu/tqr/vol17/iss2/1
Healthy People 2020. (2015). Maternal. Infant, and Child Health. Retrieved on May16,
2015, from http://www.healthypeople.gov/2020/topics-objectives/topic/maternalinfant-and-
child-health

141
Hibberts, M. F., & Johnson, R. B. (2012). Mixed methods research. In A. Briggs, M. Coleman, & M.
Morrison (Eds.), Research methods in educational leadership and management (3rd ed., pp.
122–139). Upper Saddle River, NJ: Merrill Education.
Hofman, J. J., Dzimadzi, C., Lungu, K., Ratsma, E. Y., & Hussein, J. (2008). Motorcycle ambulances
for
referral of obstetric emergencies in rural Malawi: do they reduce delay and what do
they cost?. International journal of gynecology & obstetrics, 102(2), 191-197.
Ibrahim F. H. N., Kisame, C., & Hussein, K. (2013). Security, Governance and Regional Integration:
Issues in today’s Africa. Development, 56(3), 321-327.
http://www.palgravejournals.com/development/journal/v56/n3/abs/dev201416a.html
Imo, C. K., Isiugo-Abanihe, U. C., & Chikezie, D. C. (2016). Perception of childbearing women on
gender roles
in reproductive decision making and under-five children health status in Abia State, Nigeria.
Gender & Behaviour, 14, 7040–7056.
Jacobs, B., Por, I., Bigdeli, M., Annear, P. L., & Van Damme, W. (2011). Addressing access barriers to
health
services: an analytical framework for selecting appropriate interventions in low-income Asian
countries.
Health Policy And Planning, 27, 288–300. doi:10.1093/heapol/czr038
Jacobsen, S. L., & Nielsen, J. K. (2014). Sub Saharan Africa’s underdevelopment, causes of it, and
what the
future might hold (Unpublished master’s thesis). Aarhus School of Business and Social
Sciences, Aarhus University, Aarhus, Denmark.
Jarvis, P. R. E. (2016). Improving emergency department patient flow. Clinical and experimental
emergency
medicine, 3(2), 63.
Kamgnia, B. (2006). Use of health care services in Cameroon. International Journal of Applied
Econometrics
and Quantitative Studies, 3, 53–64. Retrieved from
http://www.usc.es/economet/reviews/ijaeqs323.pdf

142
Kiguli, J., Ekirapa-Kiracho, E., Okui, O., Mutebi, A., MacGregor, H., & Pariyo, G. W. (2009).
Increasing
access to quality health care for the poor: Community perceptions on quality care in Uganda.
Patient
Preference and Adherence, 3, 77–85. doi:10.2147/PPA.S4091
Koh, H. K., & Nowinski, J. M. (2010). Health equity and public health leadership. American Journal
of Public Health, 100, S9–S11. doi:10.2105/AJPH.2010
.191379
Kruk, M. E., Porignon, D., Rockers, P. C., & Van Lerberghe, W. (2010). The contribution of primary
care to
health and health systems in low-and middle-income countries: A critical review of major
primary care initiatives. Social Science & Medicine, 70, 904–911.
doi:10.1016/j.socscimed.2009.11.025
Leina, C. Y. (2011, June). Cameroon loses ground on maternal health goal. We News. Retrieved from
http://womensenews.org/2011/06/cameroon-loses-ground-maternal-health-goal/
Levesque, J. F., Harris, M. F., & Russell, G. (2013). Patient-centered access to health
care: conceptualizing access at the interface of health systems and populations.
International journal for equity in health, 12(1), 18.
Maathai, W. (2011). Challenge for Africa. Sustainability Science, 6, 1–2. doi:10.1007
/s11625-010-0120-2
Marshall, B., Cardon, P., Poddar, A., & Fontenot, R. (2013). Does sample size matter in qualitative
research?: A
review of qualitative interviews in IS research. Journal of Computer Information Systems,
54(1), 11–22.
doi:10.1080/08874417.2013
.11645667
McTavish, S., & Moore, S. (2015). On est ensemble: Social capital and maternal health care use in
rural
Cameroon. Globalization and Health, 11(1), 1–8. doi:10.1186

143
/s12992-015-0121-0
Morales, L. S., Lara, M., Kington, R. S., Valdez, R. O., & Escarce, J. J. (2002). Socioeconomic,
cultural, and
behavioral factors affecting Hispanic health outcomes. Journal of Health Care for the Poor
and
Underserved, 13, 477–503. doi:10.1177/104920802237532
Nguefack, H. L. N., Gwet, H., Desmonde, S., Oukem-Boyer, O. O. M., Nkenfou, C., Téjiokem, M. &
Alioum, A. (2016). Estimating mother-to-child HIV transmission rates in Cameroon in 2011:
a computer simulation approach. BMC Infectious Diseases, 16(1), 1–11. doi:10.1186/s12879-
016-1336-2
Nikiema, B., Haddad, S., & Potvin, L. (2012). Measuring women’s perceived ability to overcome
barriers to healthcare seeking in Burkina Faso. BMC Public Health, 12, 147–159.
doi:10.1186/1471-2458-12-147
Nzima Nzima, V. (2014). Health sector strategy and economic development in Cameroon: History,
challenges
and perspectives (Master’s theses). Georgia State University, Atlanta, GA. Retrieved from
https://pdfs.semanticscholar.org/7c52
/39080dbc8c67b76ec85cb97b9c496c9ccc9b.pdf
Obasi, E. Z. (2013, December). A review of the barriers and socio-cultural factors influencing the
access to
maternal health care services in Nigeria (Master’s thesis). Helsinki Metropolia University of
Applied Sciences, Helsinki, Finland.
Odetola, T. D. (2015). Health care utilization among rural women of child-bearing age: A Nigerian
experience.
Pan African Medical Journal, 20(151). doi:10.11604/pamj
.2015.20.515.5845
O’Reilly, A. (Ed.). (2010). Encyclopedia of motherhood. Thousand Oaks, CA: Sage.
Parmar, P., & Agrawal, P. (2010). Report: Women’s health study, Djohong District, Cameroon.
Retrieved from

144
http://internationalmedicalcorps.org/document.doc
?id=87
Pemunta, N. V., & Fubah, M. A. (2015). Socio-cultural determinants of infant malnutrition in
Cameroon.
Journal of Biosocial Science, 47, 423–448. doi:10
.1017/S0021932014000145
Peters, D. H., Garg, A., Bloom, G., Walker, D. G., Brieger, W. R., & Hafizur Rahman, M. (2008).
Poverty and
access to health care in developing countries. Annals of the New York Academy of
Sciences, 1136(1), 161–171. doi:10.1196/annals.1425 .011
Phung, V. H., Windle, K., Asghar, Z., Ortega, M., Essam, N., Barot, M. & Siriwardena, A. N. (2014,
February). Systematic review: The barriers and facilitators for minority ethnic groups in
accessing urgent and prehospital care. Paper presented at the Meeting Challenges in
Emergency Care conference, University of Sheffield, Sheffield, England.
Poverty & Healthcare. (2013). Data retrieved from http://www.our
africa.org/cameroon/poverty healthcare
QSR International. (2013). An overview of NVivo: Software to support qualitative and mixed methods
research. Retrieved from http://download.qsrinternational.com/Resource/NVivo10/NVivo-10-
Overview.pdf.
Quick, J., Jay, J., & Langer, A. (2014). Improving women’s health through universal health coverage.
PLoS
Med, 11(1). doi:10.1391/journal.pmed.1001580
Rigg, K. K., Cook, H. H., & Murphy, J. W. (2014). Expanding the scope and relevance of health
interventions: Moving beyond clinical trials and behavior change models. International
Journal of Qualitative Studies in Health and Well-being, 9. doi:10
.3402/qhw.v9.24743

145
Rudestam, K. E., & Newton, R. R. (2015). Surviving your dissertation: A comprehensive guide to
content and
process (4th ed.). Los Angeles, CA: Sage.
Sarantakos, S. (2012). Social research (4th ed.). London, England: Palgrave Macmillan.
Sarafis, P., Rousaki, E., Tsounis, A., Malliarou, M., Lahana, L., Bamidis, P., ... & Papastavrou, E.
(2016). The
impact of occupational stress on nurses’ caring behaviors and their health related quality of
life. BMC nursing, 15(1), 56.
Schlegel, E. (2015). Community based participatory research to assess health practices in women of
childbearing age (Bachelor’s thesis). Retrieved from http://kb.osu
.edu/dspace/bitstream/handle/1811/68726/THESIS_FINAL.pdf?sequence=1
Sheikh, M., Mahamoud, A., & Househ, M. (Eds.). (2015). Transforming public health in developing
nations.
UK: IGI Global.
Shosha, G. A. (2012). Employment of Colaizzi’s strategy in descriptive phenomenology: A reflection
of a
researcher. European Scientific Journal, 8, 31–43. Retrieved from
http://www.eujournal.org/index.php/esj/article/viewFile/588/657
Smith, J. A. (Ed.). (2015). Qualitative psychology: A practical guide to research methods. Los
Angeles, CA:
Sage.
Soh, M. (2013). Access to healthcare vis-à-vis women’s reproductive health in Cameroon. Journal of
International Women’s Studies, 9(1), 117–134. Retrieved from
http://vc.bridgew.edu/cgi/viewcontent.cgi?article=1291&context=jiws
Surbakti, E. F., & Sari, K. (2018). The Relationship Between Consultation Length and Patient
Satisfaction: A
Systematic Review. KnE Life Sciences, 4(9), 41-49.
Tandi, T. E., Cho, Y., Akam, A. J. C., Afoh, C. O., Ryu, S. H., Choi, M. S., Kim, K. & Choi, J. W.
(2015).

146
Cameroon public health sector: Shortage and inequalities in geographic distribution of health
personnel.
International Journal for Equity in Health, 14, 43–54. doi:10.1186/s12939-015-0172-0
Tchombe, T. M. S., Shumba, A., Lo-Oh, J. L., Gakuba, T. O., Zinkeng, M., & Teku, T. T. (2012).
Psychological
undertones of family poverty in rural communities in Cameroon: resilience and coping
strategies. South
African Journal of Psychology, 42, 232–242. doi:10.1177/008124631204200210
Tesch, R. (2013). Qualitative research: Analysis types and software. London, England: Routledge.
Tita, A. T., Selwyn, B. J., Waller, D. K., Kapadia, A. S., & Dongmo, S. (2005). Evidence-based
reproductive
health care in Cameroon: Population-based study of awareness, use and barriers [Abstract].
Bulletin of the World Health Organization, 83, 895–903. Retrieved from
http://www.who.int/bulletin/volumes/83/12
/tita1205abstract/en/
Ukpere, W. I. (2011). Globalisation and the challenges of unemployment, income inequality and
poverty in
Africa. African Journal of Business Management, 5, 6072–6084. doi:10.5897/AJBM11.905
[Remove extra blank line]
United Nations International, Cultural, and Educational Fund. (2011). The state of the world's children
2011executive summary: Adolescence
an age of opportunity. Unicef.
Varda, D. M., Hardy, R., Millar, A., & Talmi, A. (2016). Public health, mental health and primary care
differences in urban and rural counties in a system of care for children with special healthcare
needs.
Health Systems and Policy Research, 3(3) 1–7. doi:10.21767/2254-9137.100041
Weinger & Akuri, (2007). Cameroonian women’s perceptions of their health care needs. Nordic
Journal of
African Studies, 16(1), 47–63. Retrieved from http://www

147
.njas.helsinki.fi/pdf-files/vol16num1/weinger2.pdf
Whitehead, A. L., Sully, B. G., & Campbell, M. J. (2014). Pilot and feasibility studies: Is there a
difference
from each other and from a randomized controlled
trial?.
Contemporary clinical trials, 38(1), 130-133. doi:10.1016/j.cct.2014.04.001
Whitaker, K. M., Wilcox, S., Liu, J., Blair, S. N., & Pate, R. R. (2016). African American and white
women׳ s
perceptions of weight gain, physical activity, and nutrition during pregnancy. Midwifery, 34,
211–220.
doi:10.1016/j.midw.2015.11.005
Woodsong, C., Musara, P., Chandipwisa, A., Montgomery, E., Alleman, P., Chirenje, Z. M., &
Hoffman, I.
(2014). Multipurpose Prevention of HIV and Pregnancy: Perspectives of Users, Providers and
Community Advisors in Zimbabwe and Malawi. AIDS research and human retroviruses,
30(S1), A141-
A141.
World Bank. (2011). Reproductive health at a glance: Cameroon. Retrieved from
http://siteresources.worldbank.org/INTPRH/Resources/376374-1303736328719
/Cameroon42111web.pdf
World Bank. (2013). Better access to health care for all Cameroonians. Retrieved from
http://www.worldbank.org/en/country/cameroon/publication/better-health-care
- access-for-all-Cameroonians
World Bank. (2016). Life expectancy at birth, female (years). Retrieved from http://data
.worldbank.org/indicator/SP.DYN.LE00.FE.IN
World Health Organization. (2009). Health workforce, infrastructure, essential medicines. 95-105.
World Health Organization. (2012). Health systems in Sub Saharan Africa. What is their status and
role in meeting the health millennium development goals. Retrieved from
https://www.aho.afro.who.int/en/ahm/issue/14/reports/health-systems-sub

148
-saharan-africa-what-their-status-and-role-meeting-health
World Health Organization. (2015). WHO recommendation on partnership with Traditional Birth
Attendants (TBAs). World Health Organization. Retrieved from
https://extranet.who.int/rhl/topics/improvinghealth-system-performance/who-
recommendation-partnership-traditional-birth-attendants-tbas
World Justice Project. (2013). Rule of law index. Retrieved from http://
worldjusticeproject.org/sites/default/files/malawi_country_report.pdf

