


1
Section 1: Foundation of the Study
The growing healthcare costs in the United States healthcare industry have posed
a significant challenge to individuals, insurers, policymakers, and the national GDP.
Health literacy on medical utilization is crucial and challenging to individuals with low
health literacy and healthcare organizations. Palumbo (2017) identified low health
literacy as the determinant of insufficient access to health-related services. Individuals
with inadequate health literacy are prone to not engaging in health-related information
due to low self-efficacy in understanding the information to make health decisions
(Palumbo, 2017; Simpson et al., 2020). Barello et al. (2020) recognized a primary
objective of the World Health Organization to increase the rate of patients’ health literacy.
Researchers have shown that a patient’s psychological readiness, autonomous health
commitment, and provider's encouragement determine the level of health literacy
(Graffigna et al., 2016).
Through this qualitative study, I explored the strategies private health insurance
managers use to increase health literacy on medical utilization to reduce healthcare costs.
Following are the components of Section 1, including the background of the problem, the
problem and purpose statements, the nature of the study, and the research and interview
questions. Next, I addressed the conceptual framework as a lens to discuss the problem,
operational definitions of terms for ease of understanding, and the study's significances,
assumptions, limitations, and delimitations. Finally, I wrote the literature review and
summation before transitioning to Section 2 of the study.

2
Background of the Problem
Health literacy is vital to delivering healthcare services to benefit patients,
families, health providers, and health insurance companies. MacLeod et al. (2017)
identified poor health literacy as the contributor of patients' unsatisfaction, ineffective
adherence to prophylactic medical treatment and prescription intake, increased healthcare
utilization and spending. In their study, Walters et al. (2020) showed that health literacy
interventions effectively enhance positive attitudes towards health, particularly vulnerable
populations facing health disparities. Fleary and Joseph (2020) approximated that 80
million adult Americans live with low health literacy. The financial ramification of
patients with limited health literacy on healthcare insurance organizations results in
expensive treatment payments. Through health literacy programs, managers and patients
could understand the importance of routine medical utilization for preventive outcomes
and cost reduction. Health literacy strategies to improve health literacy on patients to
understand medical utilization might improve patients' health outcomes and shrink
healthcare costs for people and organizations.
The purpose of this study was to understand strategies private health insurance
companies use to improve health literacy on medical utilization to reduce healthcare
costs. Evidence from undertaking this research might indicate a positive social change to
create a healthy initiative on adequate healthcare utilization to prevent diseases and
reduce healthcare costs. As I have presented a brief account of the background of the
study, next is the problem statement, which is the heart of the research.

3
Problem Statement
The top 5% of the population with the highest medical utilization is responsible
for 50% of the overall healthcare costs reaching a yearly average of $53,174 in the United
States (Mitchell, 2020). The national health expenditure as a percent of gross domestic
product was 17.7%, $3.8 trillion accounted for the total health expenditure, and $11,582
per individual expenses spent in 2019 (Centers for Medicare & Medicaid Services, 2020).
The general business problem was that the lack of health-related knowledge has
contributed to healthcare overutilization causing healthcare expenses to increase. The
specific business problem was that some private health insurance managers lack
strategies to increase patients' healthcare literacy on medical utilization to reduce
healthcare expenses.
Purpose Statement
The purpose of this qualitative, multiple case study was to explore the strategies
private health insurance managers use to increase patients' healthcare literacy on medical
utilization to reduce healthcare expenses. The targeted population consisted of private
health insurance managers from two health insurance organizations in Nevada who have
at least 3 years of experience effectively improving patients' health literacy on medical
utilization to reduce healthcare expenses. The findings of this study may have a positive
social change in creating health-literate individuals for improving communities' citizens'
health and reducing patient healthcare expenses.

4
Nature of the Study
The three research methods used to meet and achieve the purpose of my study are
quantitative, qualitative, and mixed methods (Yin, 2018). The qualitative research method
involves using an information-gathering approach, such as semistructured, openended
interview questions to collect data to create a nonnumerical figure (Saunders et al., 2019).
Researchers apply the quantitative method to assess variables' statistical characteristics
and relationships (Saunders et al., 2019). The mixed method is a mixture of quantitative
and qualitative approaches, which permits a researcher to address more complex research
questions and gather a deeper and more significant collection of data than a single
method (Saunders et al., 2019; Yin, 2018). The quantitative and mixed methods were not
relevant for this study because I was not seeking to confirm or disconfirm a hypothesis
about variables’ characteristics or relationships in analyzing the strategies to increase
health literacy and decrease healthcare costs. The qualitative method was the most
applicable to this study because it allowed me to explore a more indepth understanding of
how healthcare managers develop and implement strategies to enhance health literacy
while decreasing healthcare costs.
I considered four qualitative designs for the study: (a) phenomenological, (b)
ethnographic, (c) narrative, and (d) case study. The phenomenological model allows a
researcher to explore the meaning of a lived- experience from the participant's perspective
(Creswell & Poth, 2017). The design allows a researcher to focus on the meaning of an
individual's lived experience, which is not my research focus. Frey (2018) explained that
an ethnographic design identifies a group of people's social and cultural patterns in their

5
natural habitat. Ethnographic design was not appropriate for my study because the focus
was not on individuals’ and groups' social and cultural experiences.
Bingley (2020) explained that using a narrative design allows a researcher to
identify specific problems as essential to human interaction, where participants tell their
individual stories in their own words. A narrative inquiry was not suitable for my research
because individual personal stories would not help me address my research question.
Using a case study allows a researcher to get rich data and thick descriptions of the past
and current experiences concerning the topic of interest (Chini et al., 2019). Employing a
case study enables a researcher to address a real-life organizational setting in a bounded
system of daily activities used to gain knowledge and describe the organizational
phenomenon (Saunders et al., 2019). Yin (2018) explained that a multiple case study
design might be more desirable than a single case study design because using multiple
case studies allow comparison among cases. I, therefore, used a multiple case study
design for my study.
Research Question
What strategies do private health insurance managers use to increase patients'
healthcare literacy on medical utilization to reduce healthcare expenses?
Interview Questions
1. What strategies does your organization apply to help patients understand
how healthcare literacy is a part of their health benefit to mitigate
unnecessary expenses?

6
2. How do your organization’s staff members communicate health literacy
strategies on utilization to your patients to reduce healthcare costs?
3. What derivative programs have your organization implemented to improve
health literacy?
4. Based on your organization’s patients’ experiences of providing health
insurance, what are the realized benefits of consumers' health literacy
strategies on cost reduction?
5. What are the strategies your organization implemented to help increase
patient literacy to understand adequate medical utilization of healthcare to
reduce healthcare costs?
6. What are your organization’s challenges in addressing healthcare medical
utilization to reduce healthcare expenses?
7. What measures have your company implemented to quantify the
effectiveness of consumers' healthcare utilization literacy strategies?
8. What else can you add that will help me understand your organization's
strategies to increase patient's health literacy on medical utilization to
lower healthcare costs?
Conceptual Framework
The conceptual framework that applied to this study are the health belief model
(HBM) and the Andersen health service utilization model (HSU). The HBM was initiated
in the 1950s when psychologists, Hochbaum, Rosenstock, and Kegels (Hochbaum et al.,

7
1952) at the Public Health Services addressed preventive health benefit concerns
(Rosenstock, 1974). The HBM is essential and one of the models utilized in many areas
of healthcare to increase health behaviors (Krekeler et al., 2020). HBM is used as a lens
to recognize strategies to enhance providers’ or patients’ involvement in various
healthcare utilization interventions. The HBM emphasized the comprehension of health
motivational elements and the purpose for an individual’s participation and lack of
participation in undertaking programs beneficial for health (Rimer & Glanz, 2005;
Rosenstock, 1974).
Sheppard and Thomas (2021) stated that the critical propositions underlying HBM
are the following six constructs to understand an individual’s willingness to accept or
reject intervention to aid behavioral health transformation: (a) perceived susceptibility to
disease, (b) perceived severity of illness, (c) perceived benefits of behavioral change, (d)
perceived barrier to behavioral change, (e) signals to action, and (f) self-efficacy to
engage in health services. Healthcare managers can use HBM tenets to describe and
understand individuals' motivational involvement in activities to improve healthcare
utilization. Through the HBM perspective, managers can understand the specific
construct contributing to a patient’s health behavioral change and use the concept to
create intervention programs to promote behavioral transformation in patients to increase
patients' healthcare literacy on medical utilization to reduce healthcare expenses. The
HBM applied to this study for health intervention and educational precedence established
through this concept to achieve behavioral change. HBM aligned with the aim of this
study to understand how health insurance managers promote intervention strategies to

8
implement health literacy programs leading to medical utilization to reduce healthcare
expenses.
Andersen’s health service utilization framework was recognized in 1968 by
Ronald Andersen to acknowledge the shared and distinct factors to enable or hinder the
use of health services (Andersen, 2008; SoleimanvandiAzar et al., 2020). HSU
framework facilitates the understanding that three influences determine an individual use
of healthcare services: predisposing, which is an individual status and health belief,
enabling factors such as support and availability of health insurance; and need, which is
perceived and genuine need for medical services (Dang et al., 2018; Roberts et al., 2018;
Shao et al., 2018). HSU model is significant in exploring and predicting the healthcare
utilization access of an individual. Applying the HBM and the HSU as the conceptual
frameworks to this study increased understanding in exploring strategies private health
insurance managers use to increase patients' healthcare literacy on medical utilization to
reduce healthcare expenses.
Operational Definitions
Critical health literacy: Critical health literacy refers to people’s skills and
activity to manage health, personal level capabilities and actions on the social factor of
health, and the collective-level skills and measures on the social determinant of health to
accomplish better health (De Wit et al., 2018).
Functional health literacy: Functional health literacy involves the capacity of an
individual to retrieve, process, and comprehend fundamental communication and services
for good health-related decisions (Nutbeam, 2008).

9
Health literacy: Health literacy became popularized since Simonds' inception of
health literacy in 1974, many authors and organizations have presented various
definitions (Sørensen & Pleasant, 2017). In 2004, the Institute of Medicine defined
health literacy as the personal aptitude to acquire, process, and comprehend the critical
health information and services required to achieve good health decisions. Zheng et al.
(2018) categorized health literacy as health knowledge, behavior, belief, and skills.
Healthcare overutilization: Healthcare overutilization refers to the use of
healthcare facilities that provided services or products that fail to produce positive health
outcomes (Morgan et al., 2019).
Interactive health literacy: Interactive health literacy encompasses higher
proficiencies to extricate novel information, understand various communication types,
and implement new knowledge to create change (Nutbeam, 2008).
Medical/healthcare utilization: Medical/healthcare utilization signifies the
utilization of healthcare services and the explanation of individual’s health service use for
the objective of avoiding and treating health complications, increase the management of
health and welfare, or gaining information concerning an individual’s health conditions
(Gellman & Turner, 2013; National Academies of Sciences, Engineering, and Medicine,
2018).
Assumptions, Limitations, and Delimitations
Identifying the execution measures of a study involves various delineators to
explain the study, such as assumptions, limitations, delimitations, and other elements
(Burkholder et al., 2019). Stating the assumptions, limitations, and delimitations of

10
research is crucial in academic research for readers to understand how the study was
conducted. Assumptions, limitations, and delimitations are essential to enhance the
quality of the research findings and clarify the researcher's proposed evidence
(Theofanidis & Fountouki, 2018).
Assumptions
Assumptions are beliefs essential in conducting research but cannot be
substantiated (Simon, 2011). The study involves several assumptions; the initial
assumption was that the participants will answer the interview questions presented
honestly. My second assumption was that the private insurance managers at my chosen
establishment possess the knowledge and experience to use health literacy strategies to
reduce healthcare utilization. The final assumption was that using a qualitative multiple
case study will let me collect more data on what strategies private health insurance
managers implement to educate patients on achieving adequate healthcare utilization to
reduce healthcare costs.
Limitations
A qualitative study researcher must recognize limitations to the study design,
sample size, and data selection. Limitations are compulsory restrictions and constraints
which affect the research design, results, and conclusion and control any interpretations
of the outcomes (Theofanidis & Fountouki, 2018). I anticipated limitations to this study
in the possibility of participants’ responses to misrepresenting information in answering
interview questions, (participants telling me what they think I might want to hear rather
than truthful responses), which might influence data interpretation and findings,

11
Furthermore, the choice of my research design using a multiple case study with a small
sample may be a limitation for the study findings.
Delimitations
Delimitations of research are the capacity and limits that the author determines.
Delimitations focus on the conceptual research framework, general information, research
questions, sample study, and concept (Theofanidis & Fountouki, 2018). I omitted other
organizations that fit into my purposive sampling in different healthcare institutions
locally and in other states. However, other healthcare institutions could provide more
information on healthcare organizations' strategies to educate patients on utilizing
healthcare services to reduce healthcare costs. Another delimitation was the small sample
size and the geographic setting restricting the study result's transferability to other
healthcare locations. The delimitations mentioned above may influence the internal
validity of my study.
Significance of the Study
This qualitative multiple case study's potential significance to healthcare
managers was to provide them with a tool to develop strategies to reduce expenses. As
healthcare literacy increases, healthcare costs can probably decrease through patient
education (Gossett et al., 2019). My study's potential significance to social change
involves improving patients' knowledge of health practices to advance adequate
healthcare utilization, starting from advocating preventive lifestyle, reducing patients’
need for medical care.

12
Contribution to Business Practice
Shrank et al. (2019) specified that the approximated worth of waste in the U.S.
healthcare system ranged from $760 billion to $935 billion, accounting for an estimated
25% of overall healthcare spending. Gossett et al. (2019) forecasted approximately $1
trillion of total waste in the U.S. healthcare system. The predicted hidden savings from
interventions that lower waste, excluding savings from administrative ramifications,
ranged from $191 billion to $286 billion (Shrank et al., 2019). This amount figure
exemplifies a potential 25% reduction in the total cost of waste (Shrank et al., 2019;
Sisko et al., 2019). Therefore, the findings from this study could contribute to the cost
reduction strategies by enabling healthcare managers to improve healthcare literacy for
reducing the utilization rates in the healthcare industry.
Implications for Social Change
This study's implication for positive social change relates to helping individuals
become responsible through a health literate approach for improving their health and
wellbeing. Health literacy can improve health communication understanding and
decrease healthcare costs for consumers, private insurance businesses, and society,
closing gaps in finding healthcare remedies to reduce healthcare costs. Additionally, this
study's findings might enable policymakers to enforce health literacy policies, bringing
greater awareness to social entrepreneurs for further health literacy initiatives to benefit
the low-health literate population to acquire health-related knowledge.

13
A Review of the Professional and Academic Literature
A researcher in their literature review aims to identify, analyze, and synthesize
adequate literature essential to health literacy intervention strategies. In this qualitative
multiple case study, the goal was to explore the strategy private health insurance
managers use to increase health literacy by interviewing managers who deal with patient
intervention programs in health insurance organizations in the urban community in
Nevada. Through this literature review, I explored numerous data related to describing
how health literacy intervention strategies will aid in understanding medical utilization to
reduce the overall higher healthcare costs in the United States.
An effective academic literature review consists of a concise central point, the
analysis, and the synthesis of evidence established on the issue (Linnenluecke et al.,
2020). Evaluating literature encompassing patients' healthcare literacy on medical
utilization to reduce healthcare expenses might present beneficial strategies other
managers can apply to mitigate healthcare costs effectively. Therefore, in this literature
review, the use of relevant literature and conceptual framework on the health belief model
developed an understanding of the existing seminal work conducted on this topic. The
review process involved searching for many references comprising peer-reviewed
journals, books, and government health agencies within 5 years of study completion.
Literature Review Search Strategy
The literature evaluation strategy employed in this study encompassed the
primary topic and other search terms involving healthcare costs, health literacy, low
health literacy, healthcare or medical utilization, and the health belief model. To

14
complete the literature review section for this study, I gained access to various search
databases through the online library and Google Scholar search. The search contribution
involves Walden University library databases, such as CINAHL & MEDLINE, Academic
Search Complete, ProQuest Health & Medical Collection, SAGE Knowledge,
ScienceDirect, EBSCOhost, Elsevier, and other helpful databases. Google Scholar
provided easy access to multiple articles with a link to retrieve journals available at the
Walden library. Based on the Walden University DBA restriction on the use of articles
within 5 years of graduation, I selected articles ranging from 2018 to 2022. Furthermore,
the pieces from the government agencies databases made up part of healthcare
organizations' contributions, such as the Agency for Healthcare Research and Quality
(AHRQ), Centers for Medicare and Medicaid Services (CMS), and Institute of Medicine
(IOM). Table 1 illustrates the distribution of the literature reviewed, consisting of books,
peer-reviewed, and non-peer-reviewed journals used for the study.
Table 1
Sources of Professional and Academic Literature
Review Review
References References Percentage of the of the
published published (%) Total literature literature before
in or after published references
Sources before after
2018 2018
2018 2018
Peer-
reviewed
Journals
Non-
13
70
23
70
85
176

15
peer-
reviewed
Journals
3
3
8
10
15
24
Books
2
6
5
3
0
16
Total
18
79
36
83
100
216
Note. Frequency and percentage of resources within the literature review and proposal.
Conceptual Framework: Health Belief Model
In this qualitative multiple case study, I used the HBM as a framework to identify
and understand how managers develop and implement effective health literacy strategies.
Skinner et al. (2015) identified the importance of the HBM in understanding why patients
refused to screen for tuberculosis when offered access to traveling X-ray vans.
Understanding the HBM might enhance patients’ health experiences to lessen preventable
diseases and higher healthcare costs related to healthcare overutilization. According to
Rosenstock (1966), the HBM is a popular model in health advancement interventions to
support justification to defend reasons people accept or reject preventive health
initiatives. Green et al. (2020) identified HBM as essential to interventions to strengthen
the understanding of health challenges, improve perceptions of individual risks, support
actions to reduce or eradicate the risk, and develop a sense of self-efficacy to initiate
change. The HBM creates an understanding that healthcare providers and patients need to
increase adequate healthcare utilization techniques to detect disorders early to avoid the
onset leading to suffering, diseases, and higher healthcare costs.
The HBM promotes an understanding of numerous beliefs that enable individuals
to seek medical care. In recognition for individual’s beliefs, Skinner et al. (2015) pointed
out several principles of the HBM indicating individual’s expectations to participate in a
health behavior in a rational calculation of self-interest if they consider: (a) the risks for

16
an illness, (b) a disorder with an impending severe outcome, (c) health mediation with a
positive outcome, (d) benefit for engaging in action, and (e) cost-benefit analysis on
perceived barriers. These factors are vital to identifying patients’ impediments or
motivation for participating in healthcare services (Skinner et al., 2015). The principles of
the HBM enable health managers to facilitate the implementation of strategies to increase
patients' healthcare literacy on medical utilization to reduce healthcare expenses.
Several studies have presented important data to demonstrate the impact of HBM
on mitigating the problem of various illnesses through behavioral transformation, creating
mindfulness, and precautionary practices. An example was a study applying the HBM
constructs in a survey that positively influenced nursing students' consciousness
concerning COVID-19 mitigation strategies (Elgzar et al., 2020). Similarly, another study
portrayed workers’ awareness concerning the 2012 coronavirus Middle East respiratory
syndrome (MERS-Cov) infection and the intervention of the Saudi Ministry of Health in
accomplishing significant growth in creating responsiveness through the application of
HBM (Alsulaiman & Rentner, 2018). These studies proved the significance of applying
HBM in other areas, such as health literacy intervention, to promote adequate medical
utilization and reduce the higher healthcare expenses associated with the lack of health
knowledge.
HBM might help health insurance managers, patients, policymakers, and scholars
to explore many interventions needed to influence citizens to increase health literacy on
medical utilization to improve health and reduce costs. Health insurance managers can
use HBM to understand many propositions of health literacy to produce the best health

17
literacy programs to benefit patients. For example, Mohebbi et al. (2019) conducted a
study to demonstrate a positive impact of initiating health literacy intervention focusing
on the advantages of self-management of expecting mothers with gestational diabetes.
Mohebbi et al. confirmed that patients who received educational training in
selfmanagement of diabetes improved their knowledge through the HBM intervention.
Health literacy intervention might be beneficial to other diseases and a motivator to a
patient in understanding proper medical utilization for early disease detection and
opportunity for cure.
The History and Development of the HBM
In the early 1950s, public health professionals’ objectives focused on
understanding why individuals avoided preventive measures of diseases such as polio
(Rosenstock, 1974). I preferred the HBM as a conceptual foundation to comprehend the
factors attributable to health decision-making involving patients' behaviors seeking
preventive remedies and adequately utilizing healthcare services. The founders of the
HBM focused on many intervention projects and patients’ reactive actions based on the
HBM six constructs in understanding the trigger for healthcare or medical utilization and
its impact on health. Many of the HBM tenets are proven to be successful in forecasting
health advancement behaviors (Luquis & Kensinger, 2019). Healthcare managers might
use HBM to develop programs to improve people’s health literacy relating to the
perceived barrier to disease and the perceived benefits in mitigating the onset of illness.
Understanding the HBM supports many good health habits to achieve healthy
wellbeing. Additionally, motivating elements play a crucial part in individual daily

18
conduct by numerous influences such as educational level, financial status, and
geographic location (Louis, 2019). Kurnia et al. (2021) identified behavior as an element
contributing to awareness, attitudes, and beliefs. Relatedly, Louis (2019) confirmed that
the immediate attention of the HBM depends on the attitude and people’s belief about
effort concerning health. Louis conducted a study applying the HBM constructs to
understand the behaviors of Haitian men on prostate cancer screening. Louis found that
cultural belief was detrimental to the lack of cancer screening for Haitian men. The
suggestion that improving health literacy intervention would offer significant insight into
problems of low health screening in populations with high disease susceptibility is vital
(Louis, 2019). Vahedian-Shahroodi et al. (2021) reported a result consistent with findings
in Louis’s (2019) study that improving health education through the HBM was significant
in behavioral change in a study of children’s nutritional intervention with parents and
teacher’s support. Healthcare managers’ tasks to support patients in improving health
knowledge through health literacy programs are crucial in mitigation strategies to achieve
positive health results.
Additionally, people use various HBM constructs to assess health conditions in
seeking preventive help (Kurnia et al., 2021). An example, perceived susceptibility
enables an individual to understand the possibility of becoming sick with a disease
(Sharma, 2021). Health science researchers have documented several studies to prove the
impact of HBM application in changing individuals’ beliefs based on the behavioral
perception of health (Kurnia et al., 2021). Directing patients' behaviors to adequately
utilize healthcare services might prove beneficial to patients, healthcare providers, and

19
health insurance providers in preventing diseases that might become terminal in causing
patients' death and contributing to the rising expense of healthcare in the United States.
Researchers can use HBM to address patients’ health literacy on adequate
healthcare utilization in creating the understanding that might enable patient participation
in numerous health literacy interventions to improve health and reduce higher healthcare
costs in the long run. The paradigm of HBM presents the understanding of various
motivators to encourage individuals into partaking in health-related decisions in
adherence to adequate healthcare utilization to prevent illness. Luquis and Kensinger
(2019) suggested that the six health belief model constructs are essential to justify an
individual’s reaction to prevention, screening, and other health behaviors. Healthcare
managers can create health literacy programs to escalate adequate medical utilization
through the views of HBM six constructs: perceived susceptibility, perceived severity,
perceived benefit, perceived barrier, cues to actions, and self-efficacy to improve health.
Six Main Tenets of the HBM
HBM tenets have inverse relationships in predicting what position an individual
takes in making health decisions. Sadeghi et al. (2018) opined that many studies found
perceived susceptibility and severity to result in a health threat. Consequently, there is an
inverse relationship between perceived susceptibility, perceived severity, benefits, and
barriers, confirming that, as the perceived susceptibility decreases as the perceived
severity increases, the perceived barrier decreases, boosting motivation to not accept
protective health actions (Sadeghi et al., 2018). The six HBM tenets implementation
describes and creates an understanding of the possibility of an individual participating in

20
interventions to promote self-motivational involvement in activities to strengthen good
healthcare utilization behaviors or it also might help to explain why some healthcare
professionals choose not to at the same time (Luquis & Kensinger, 2019).
Perceived Susceptibility
Mohebbi et al. (2019) explained perceived susceptibility as one of the health
belief model constructs encompassing an individual’s belief of acquiring a disease
associated with certain behaviors endangering health. An individual is triggered to
participate in a preventive remedy when perceived health risks of contracting an illness
that could be preventable. An example is the perception of health risks prior to
participating in screening for communicable and noncommunicable diseases. Luquis and
Kensinger (2019) demonstrated that utilization of preventable care increased with
perceived susceptibility of associated health results of a particular illness screened.
Patients without the knowledge of susceptibility to diseases cannot understand and
engage in adequate medical utilization due to limited health literacy and cannot make
health-related decisions.
Larki et al. (2018) reported the impact of perceived susceptibility on reduced salt
intake and nonsmoking adherence in study participants. The application of perceived
susceptibility to this study involves health insurance managers identifying vulnerable
populations and their literacy levels. Healthcare managers can increase health literacy on
obtaining adequate medical utilization by explaining why a patient should seek medical
help to avoid the severity of illness. Additionally, a patient might reduce the risk of

21
suffering or paying higher healthcare expenses in treating preventable conditions through
health literacy intervention.
Perceived Severity
In the condition of perceived severity, individuals' beliefs may result in health
harm due to a particular behavior (Sharma, 2021). Perceived severity refers to the
propensity to reduce behavioral risks associated with the negative consequences of
disease severity originating from the medical data and individual’s knowledge (Hayden,
2017; Janz & Becker, 1984). An illustration describing perceived severity might involve
an individual with comorbidity involving hypertension and diabetes of higher-thannormal
blood levels identify a health threat triggering cues to action to reduce the severity of the
disease consequences. Implementing health literacy intervention to create an
understanding of various health self-manageable disorders will create perceived health
benefits. Perceived severity applies to identifying and tackling the effects of the danger
and the situation (Sharma, 2021).
Perceived Benefits
A patient’s understanding of perceived benefits fosters initiation to accept
healthcare services. A perceived benefit is to ensure the mitigation of behavioral
riskbenefit for acting on the perceived severity of sickness detrimental to health (Sharma,
2021). The application of perceived benefits to behavioral change describes interventions,
strategies, location, possible outcomes, and the positive impact of the behavior. Hayden
(2017) and Janz and Becker (1984) proposed that a person observes the importance and
effectiveness of implementing new behaviors to curtail the dangers of sickness and will

22
probably assume different behaviors centered on the insights of their welfare in lessening
dangers. Understanding the perceived benefit of engaging in adequate medical utilization
through health literacy initiatives enables sufficient health checks to reduce healthcare
costs.
Perceived Barriers
A perceived barrier is the obstruction of an individual belief that impedes
implementing a new intervention to enhance health conditions (Sharma, 2021). Perceived
barriers might be health insurance coverage, affordability, cultural belief, socioeconomic
status, and other factors. Luquis and Kensinger (2019) stated that the Affordable Care Act
of 2010 enhanced the opportunity of primary care access, however lessening barriers for
young people to receive health plans and prophylactic measures. Managers must
recognize and mitigate perceived barriers by expressing guarantee, enticement, and
support in health behaviors.
Janz and Becker (1984) presented perceived barriers as the utmost prevailing
element of HBM that enables people to examine the potential challenges encountered
when making behavioral change. A perceived barrier might be the cost of treatment
which (Sheppard & Thomas, 2021) stipulated that when the perceived barrier rises, an
individual’s possibility of partaking in a beneficial health conduct decline. Perceived
barrier applies to this study in explaining and understanding why many people avoid
engaging in healthcare services due to various impediments. Sheppard and Thomas
(2021) demonstrated how perceived barriers influenced COVID-19 infection prevention
based on cultural differences and other factors. Healthcare managers must find ways to

23
reduce the perceived barriers to adequate healthcare utilization to increase perceived
benefits.
Cues for Action
Another HBM constructs important for health intervention to achieve a behavioral
improvement is cues for action. Elgzar et al. (2020) identified that cues for action are a
developmental inducement to make behavioral health changes. Cues to action originate
from the pressure to act on the information related to health diagnosis (Sharma, 2021).
Alsulaiman and Rentner (2018) added that cues to action involve external and internal
stimuli. External cues consist of incidents, persons, mass media, health providers, and
other external stimuli influencing altered behaviors (Hayden, 2017; Janz & Becker,
1984). An internal cue to action is the psychological factors involving pain and signs that
motivate a person to seek help to positively influence behavioral change toward health
conditions (Janz & Becker, 1984). Cues for action might result in intervention leading to
healthcare services utilization.
An abnormal diagnosis that represents cues for action will trigger a person to seek
healthcare services to obtain a perceived benefit to reduce susceptibility and severity of
an illness. Alsulaiman and Rentner (2018) concluded in their study that individuals with
higher marks on cues to action and the other four HBM constructs followed health
recommendations when compared to the others with low results. HBM is essential to
health literacy education intervention to develop knowledge and create awareness that
might lead to action cues to prevent health problems and reduce healthcare costs.

24
Healthcare managers might apply cues to action by offering information, intervention,
and reinforcement to initiate inclination for the individuals to act.
Self-Efficacy
A significant HBM construct that enables individuals to make changes in
selfefficacy is also important to understand. Self-efficacy depends on the self-assurance
of a person's capability to act on the intervention to change behavior to improve health
(Sharma, 2021). Mohebbi et al. (2019) stated that the HBM enables an individual with
perceived susceptibility and severity to act with conviction to participate in healthy
behavior, selecting the best option to achieve an outcome while considering perceived
barriers and benefits should trigger an inducement to stay healthy. Hayden (2017)
indicated that studies proved a relationship between the capability, skillfulness of
accomplishing a goal, and goal realization. Managers can enable individuals to obtain
self-efficacy through health literacy projects to comprehend proper medical utilization,
direction, and effective reinforcement to reduce diseases and the increasing healthcare
costs.
The application of HBM and its constructs to this study explains the problems
individuals consider in taking health initiatives to improve health. Understanding an
individual’s perception through the various HBM constructs is instrumental in educating
patients on preventative self-health management (Mohebbi et al., 2019) to reduce
personal and health insurance expenses. Furthermore, HBM is an essential framework in
presenting manager’s health literacy strategies to increase adequate healthcare utilization

25
(behavior change) and reduce cost. Some healthcare expenses emerging from
underutilization of preventive care resulting from negligence, might increase healthcare
costs in the near future which is necessary to curtail the occurrence of a problem illness
through health literacy intervention.
Additionally, HBM based intervention enable various perceived triggers to enable
appropriate health decisions. An individual who understands the seriousness of an illness
must seek help to treat or cure the disease. An individual can attain health belief
advantage by engaging in programs to understand numerous valuable resources provided
to patients through research participation (Mohebbi et al., 2019). Mohebbi et al. (2019)
conducted a study to demonstrate the application of the HBM constructs on pregnant
women with gestational diabetes mellitus and found that health literacy education was
helpful in behavioral change through HBM constructs.
Healthcare stakeholders and partners are health role models in taking initiatives
with the HBM framework to create knowledge and understanding to reduce low health
literacy to increase profitability. The application of HBM and the corresponding
constructs is to achieve advanced level health literacy among healthcare users who seek
health insurance from providers. The achievement involves earlier screening and
treatment, medication adherence, understanding health disparities, and understanding
each population at their level of health literacy to mitigate perceived barriers to increase
health literacy.
Sadeghi et al. (2018) pointed out that researchers have identified education as
highly efficient in instructional programs using the HBM. The report of Sadeghi et al.’s

26
study provided evidence that HBM application in health educational training improved
knowledge in standard precautional measures in emergency departments. Alsulaiman and
Rentner (2018) recounted several successful studies conducted for various illnesses
through HBM based intervention programs. Health literacy education might create
understanding on adequate medical utilization to improve preventive care and reduce
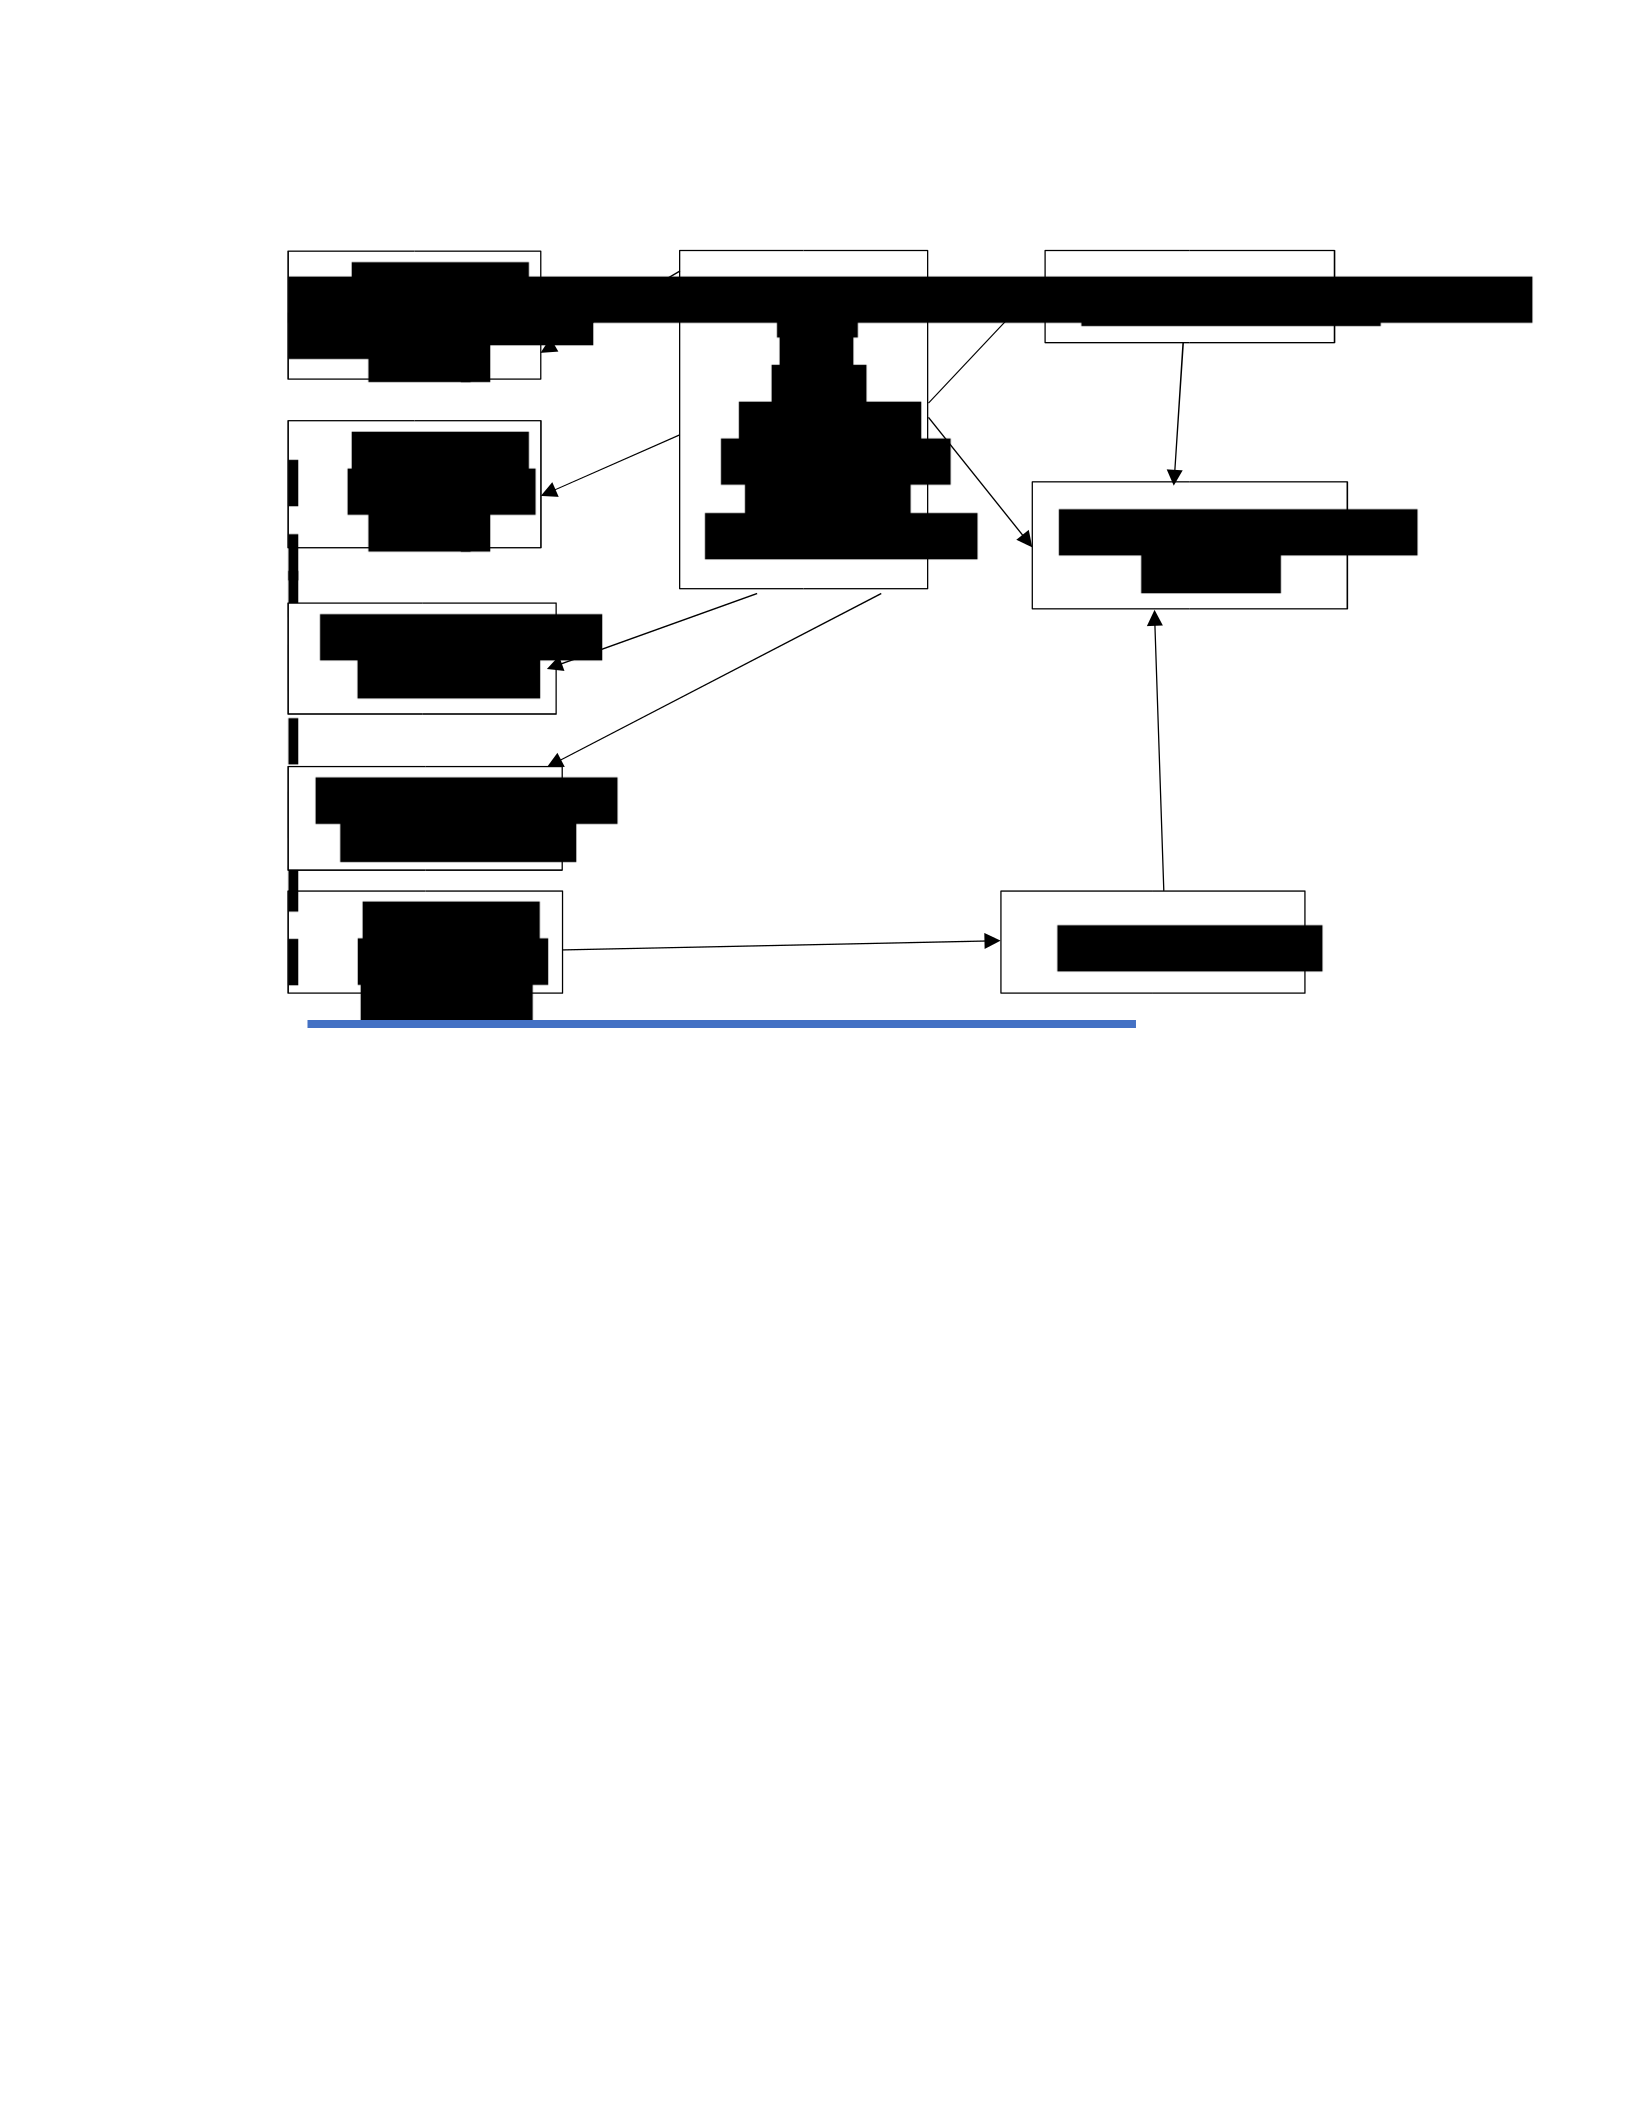
healthcare costs. The health belief model framework (see Figure 1) presented an essential
tool for explaining how HBM constructs can lead to behavior intention in healthcare use.
Individual perceptions based on the modifying elements might prompt behavioral health
activities (Rosenstock, 1974).
Figure 1
The Health Belief Flow Chart
Individual
Perception
Modifying Variables
Likelihood
of Change
27
Figure 1: Feedback loops in the HBM Model to improve the strategies
for utilization effectiveness -(Hochbaum et al., 1952)
Andersen Health Service Utilization Model (HSU)-Supporting Theory
I chose the Andersen health service utilization model (HSU) as the alternative
theory to explain the concept of health services utilization for this study’s topic. This
model was established in1968 by Ronald Andersen to understand the collective and
individual components of health service utilization (Andersen, 2008; SoleimanvandiAzar
et al., 2020). The intentions of Andersen’s HSU model focus on the determinants of
health services utilization which have three important influences with individual and
contextual equivalent: (a) enabling factors, (b) predisposing factors, and (c) need
discrepancies (Andersen, 2008; Roberts et al., 2018; Shao et al., 2018).
ealth bel
Perceived
susceptibility to
disease
Age
Sex
Race
Education
Individuality
Ethnicity
Socioeconomic
Perceived
benefits of
utilization
Perceived Threat
Cues to Action
Potential Behavioral
Change
Perceived
severity to
disease
Self-efficacy on
utilization
Perceived barrier
on utilization

28
Enabling factors are significant in determining access to health service utilization
(SoleimanvandiAzar et al., 2020). These factors encompass various levels, such as
personal, which involves salary, health insurance, wealth, and healthcare foundation.
SoleimanvandiAzar et al. (2020) added the contextual level, which comprises health
insurance exposure, community gross domestic product (GDP), healthcare workers,
location dissemination, and other variables. Additionally, enabling influences to comprise
family encouragement, health insurance plan assortment and fees, and an individual’s
community (Shao et al., 2018). Enabling factors must be challenging for healthcare
workers to identify to provide better adequate health literacy programs tailored to the
patient and the community’s needs. Health insurance managers need to consider enabling
factors of individual patients to understand the impact of health service utilization to
provide financial services with better health outcomes for patients.
Predisposing factors are crucial for health insurance managers to understand to
accomplish adequate health service utilization to avoid expensive health coverage leading
to financial loss. Shao et al. (2018) and SoleimanvandiAzar et al. (2020) described
predisposing factors involving social demographic factors such as age, sex, race, health
belief, a marital status that influence the need to seek health assistance.
SoleimanvandiAzar et al. presumed need dynamics as variables regarding observing a
person’s health status modification. Roberts et al. (2018) observed stability in health
service use based on self-evaluated health condition, comorbidity, frailty, length of
symptoms, and common mental disorder. Need discrepancy concerns perceived and an
authentic necessity for people’s desire to access healthcare service and the self-observed

29
health status have been found to also effect healthcare utilization decisions (Shao et al.,
2018; SoleimanvandiAzar et al., 2020). Observing patients will enable understanding in
assessing a patient’s HSU need factors, particularly a change in health status involving
prevailing health conditions leading to higher or sometimes, lower usage.
Andersen’s HSU model supports the medical utilization aspect of this topic. I used
this model as an alternative framework for this study to understand health insurance
providers’ strategies to increase healthcare utilization through health literacy intervention
to achieve lower healthcare costs. The HSU model applies to understanding the
fundamental elements in the utilization of healthcare resources. SoleimanvandiAzar et al.
(2020) found that the enabling, predisposing, and need factors influenced making
decisions and gaining access to healthcare services. Andersen’s HSU model supports the
HBM by explaining that healthcare utilization is influenced by predisposing needs and
enabling factors. The Andersen health service utilization model is a lens that health
insurance managers might use to enrich their knowledge of the determinants of healthcare
utilization.
Complexity Theory-Contrasting Theory
I selected complexity theory as the contrasting theory for this study. Complexity
theory gained momentum with a group of scholars from multiple fields in the 1980s with
the establishment of the Santa Fe Institute (Pascale, n.d.). This model embodied extensive
movement encamped innovative principles concerning complex adaptative systems
(Schneider & Somers, 2006). Turner and Baker (2019) proposed that organizations must
cope with the increasing complexity in human resources accessible to firms and view

30
competent and unqualified workers’ problems through the lens of the proliferation of
complexity science. Complexity science adapts to innovative leadership and management
skills, and the organization is complex (Turner & Baker, 2019).
Complexity theory: An umbrella expression that shelters fundamental philosophies
of systems-thinking, socio-technical system theory, and complex adaptive systems (CAS;
Ferreira & Saurin., 2019). These components enable organizations to adapt to
environmental pressure and sustain balance (Turner & Baker, 2019). Kallemeyn et al.
(2020) revealed that complexity theory interrupts the idea of accomplishing change due
to its unpredictable nature, and similar outcomes are not guaranteed. Understanding
complexity theory is vital in comprehending how organizations achieve change,
sustainability, and reformation. Turner and Baker (2019) addressed that this theory
perceived the system as nonlinear and unpredictable as applied to the mathematical
example of linear and predictable nature when observing the chaos.
As a focus on organizational activities over time of various categories of systems
(Rosenhead et al., 2019). Complexity theory consists of nonlinearity, the non-directional
nature of systems (Kallemeyn et al., 2020), system interdependence, and dynamic
connectivity through feedback loops (Cilliers, 2002). Emergence is the ability of a
complex system to be more significant than the total of its established segments (Manson,
2001), unsolidified boundaries, and the irregularity of particular behavior inside a
universal structure of anticipated behavior (Rosenhead et al., 2019), and diversity,
incorporating various entities of the system (McLean et al., 2021).

31
Complexity theory is essential to all organizations in understanding the
relationships between the systems and components. Spoor and Rothman (2021) hinted
that agent and system are an interdependent fundamental segment of complexity theory,
and agents should initiate an approach to enhance healthcare organizational systems to
achieve positive outcomes. Albeit complexity theory supports the dynamic nature of the
healthcare organizations, I will not be using complexity theory for my study because the
lens to view this study was not to explore the relationship between the system and its
interactions. The HBM and the Andersen model should help me identify effective health
literacy strategies that patients can use to enhance their health experiences to lessen
higher healthcare costs.
Synopsis of U.S. Healthcare Costs
Historically, there has been constant debate and policy change on healthcare in the
United States, mainly focusing on cost control. The healthcare debate is constantly on
prescription drugs while healthcare service utilization bears the highest expenses receive
less attention (Kirson et al., 2020). The condition of the U.S. healthcare costs is alarming,
knowing that the expenses do not equate to continuous positive health outcomes (Kirson
et al., 2020). Currently, the U.S. national spending on healthcare is close to $4 trillion,
signifying approximately 20% of gross domestic product (GDP; CMS, 2020). Blendon et
al. (2019) found that the United States contributes more financially to the healthcare
system when compared to other developed countries. Additionally, more Americans
understand that healthcare services are over-priced, which causes economic disability to
individuals and families in meeting household obligations (Blendon et al., 2019). Gossett

32
et al. (2019) and Kirson et al. (2020) added that in spite of the higher spending in the
United States, the value of the high cost is questionable and needs to be addressed by
healthcare policy makers.
Bringing awareness to the prevailing concern is important as healthcare costs
continue to rise for the population as a whole. The alarming truth was that Garg (2020)
analyzed the economic health of the United States, identifying the prevailing healthcare
expenditure drivers, outcomes, healthcare return on investment, and public opinion
important to citizens. Garg (2020) conducted several surveys and found that the most
significant drivers of healthcare expenses were pharmaceutical drug prices and hospital
utilization. Additionally, Garg included that more than 90% of Americans prioritized
decreasing healthcare expenses and observed that hospitals, health insurance, and
pharmaceutical companies disregarding overutilization contributed to the rising
healthcare costs. Healthcare costs and reforms have constantly become topics of debate
on finding a compromise for the contributing players in the healthcare system.
Higher healthcare costs are concerning and do not equate to better health
outcomes to some groups of the U.S. populations. Lyford and Lash (2019) addressed
critical concerns of the United States population concerning their health expenses. Lyford
and Lash postulated that Kaiser Family Foundation reported that the burden of
unsustainable healthcare costs on individuals and organizations leads to medical
bankruptcies. More people consider preventive medicine essential to health and longevity
(Garg, 2020). Education is the basis to obtain better preventive care to improve
wellbeing; health literacy intervention is essential to this process. Government support

33
ensures lower prices to promote primary care and advocate for price transparency and
rivalry to decrease medication costs (Garg, 2020). Bush (2018) identified the problems
associated with healthcare's rising costs as not addressing the systematic inequalities and
social issues that created poor health and health inequities in the United States. Bush
indicated that the United States spends over $3 trillion annually, the highest in healthcare
than other countries in the Organization for Economic Co-operation and Development
(OECD). The United States fails to produce the highest health results and does not
provide universal health care for all of its citizens in spite of the high healthcare
spending.
The most vulnerable section of the U.S. population with unaffordable healthcare
cannot afford their prescription drugs (Lyford & Lash, 2019). Lyford and Lash (2019)
added that the Center for Medicare and Medicaid reported that the United States has the
most expensive healthcare costs globally, with total spending of over $10,000 in 2017 per
person, and still rated the lowest inadequate health compared to many developed nations.
Furthermore, Lyford and Lash identified strategies to sustain healthcare costs, such as: (a)
implementing policies to reduce prescription drug prices and (b) implementing
valuebased healthcare with value-model compensation.
Haslam et al. (2019) conducted a cross-sectional systematic review to investigate
the factors contributing to the healthcare costs and the groups of organizations answerable
to attributable characteristics to the problem of the increasing healthcare costs in the
United States. Based on the review, Haslam et al. used Google Scholar to identify 225
drivers, and PubMed journal attributed the increasing healthcare costs to 47 possible

34
drivers. Haslam et al. observed divergence between the public's views concerning the
organizations or individuals responsible for the high healthcare costs' roots. Haslam et al.
(2019) found that health insurance providers attribute a sizable aggregate to the rising
costs of health service. Haslam et al. acknowledged through PubMed journals that
individuals' lifestyles, atmosphere, and medical complications were the common
established reasons for the rising cost of healthcare, without attribution to any group,
medications, or devices. The authors also found from the Google news evaluation that
hospitals and others contribute to the high cost of healthcare. Haslam et al. made a
significant conclusion that the apportioning of liability for the rising healthcare costs is
inconsistent with actual healthcare spending. Among all the problems of higher
healthcare costs, health literacy is important in understanding adequate healthcare
utilization to reduce medical costs.
Health Literacy
Health literacy increasing research and practice areas essential in building health
skills in making health-related decisions to improve good health and healthy lifestyle in
the current century (Nutbeam, 2008). According to various surveys conducted in a few
countries around the world, limited health literacy is prevailing universally. The
International Union for Health Promotion and Education (IUHPE) has recognized the
essence of health literacy advancement in communities through healthcare sponsors and
partners (Nutbeam et al., 2018b). Fleary and Ettienne (2019) stated that among the
pervasiveness of health literacy in the U. S., limited health literacy individuals encounter
racial, low economic status, poor education, aging population with special needs,

35
language barriers, ethnic challenges, and rural location restrictions. The United States has
an estimated 80 million adults with inadequate health literacy (Prince et al., 2018).
Various authors defined health literacy in many ways expressing similar concepts
and understanding. In 1974, health literacy became important in understanding how to
improve health knowledge through education, the healthcare system, and media on
upholding and sustaining wellbeing from early elementary school level (Schwartzberg et
al., 2005; Simonds, 1974). Parker and Ratzan (2019) explained that health literacy, as
recognized by the Healthy People 2030 agenda and the Health and Human Services
(HHS) concerns the suggestion and need for innovative definitions to incorporate specific
terms. Other authors affirmed that health literacy provides adequate health information
and service accessible and understandable to apply to healthcare choices and participation
in activities (Secretary’s Advisory Committee on National Health Promotion and Disease
Prevention objectives for 2030., 2019). Brach and Harris (2021) suggested that healthcare
organizational leaders should involve other health providers to develop a health
information knowledgeable organization with the goal to implement Healthy People 2030
inclusion of the health literacy proposal encompassing organizational awareness in
creating impartial opportunities for each patient.
The Institute of Medicine (2004) proposed the most significant models of health
literacy involving cultural and conceptual comprehension, print health literacy, spoken
health literacy, and numeracy. Ratzan and Parker (2000) expressed the original definition
of health literacy adopted by the IOM in 2004 as the degree to which individuals can
obtain, process, and understand basic health information and services needed to make

36
appropriate health decisions. Kickbusch et al. (2006) added that health literacy is the
capacity to construct comprehensive health choices in the setting of normal life,
domestic, communal, at the job place, healthcare organization, the marketplace, and the
legislative ground. Additionally, Kickbusch et al. suggested that health literacy is a
significant liberative approach to expanding society's power concerning their well-being,
ability to obtain information, and power to gain culpability. The importance of identifying
numerous definitions of health literacy was to create more understanding on the topic of
this study and its impact on individuals and the costs to society.
Karl and McDaniel (2018) identified that researchers who specialized in health
literacy studies locally and worldwide warned that treating individuals as possessing
adequate health literacy might prove detrimental to health. Therefore, healthcare workers
and managers should empower themselves with adequate health literacy to understand the
impact of low health literacy on healthcare costs and health outcomes. National Institutes
of Health (2014) estimated the economic burden contributed from low health literacy to
range between $106 billion to $236 billion yearly. More emphasis on addressing the
financial implications of low health literacy to healthcare organizations and health
insurance providers is crucial in reducing costs.
Various health interventions to address an individual’s level of health literacy
might involve education from the grassroots to eradicate inadequate health literacy. In an
attempt to reduce low health literacy, the Agency for Healthcare Research and Quality
(2020) adopted the Health Literacy Universal Precautions (HLUP) to direct healthcare
professionals on steps to follow when consulting with every patient. The HLUP stipulated

37
that healthcare providers must assume that all patients have low health literacy and
cannot communicate and understand health information (Killian & Coletti, 2017).
Sentell et al. (2020) presented the significance of individuals, community, and
population wellbeing knowledge, explicitly considering the impact of the global health
pandemic. Sentell et al. identified that low health literacy is influential in the worldwide
COVID-19 involving lifestyle behaviors, family association, organizational actions,
policy decisions, national mortality statistics, and the global economy. Sentell et al. study
findings suggested that adequate health literacy must be incorporated into the population
resources as a part of the community strength to support the health literacy initiative.
The authors critically addressed the implication of investing in health literacy,
considering the impact of the global COVID-19 health understanding on people (Sentell
et al., 2020). To support Sentell et al.’s (2020) assertion on achieving sufficient health
literacy, Košir and Sørensen (2020) proposed that improving public health literacy
involves increasing shared awareness of healthcare stakeholders, enabling populations
and health consumers, as well as involving patients in proactive interventions through the
healthcare organizations. Additionally, Košir and Sørensen believed that patients and
healthcare organizations are the keys to progressive outcomes on health literacy
intervention, such as the SARS-CoV-2 virus and other health debilitating encounters.
Bartsch et al. (2020) examined the financial impact of the COVID-19 pandemic
on individuals and the national level using a Monte Carlo simulation model. The model
predicts a cost of over $3000 for an individual and a national cost of over $163 billion for
the entire pandemic period. Bartsch et al. explained that COVID-19 would create a

38
financial impact on the United States healthcare system. Health care professionals and
lawmakers feared that the current capacity could be overwhelmed, and extra resources
might be needed. Asmundson and Taylor (2020) advised that low health literacy
subsequently results in more disease issues, occurrence issues, and persistence. Refining
health literacy might indicate health information knowledge on disease prevention,
enhance longevity, and increase health outcomes (Asmundson & Taylor, 2020).
Types of Health Literacy
Nutbeam (2008) identified three types of literacy skills established through proper
education and informal individual proficiencies: functional, interactive, and critical.
Nutbeam (2008) and Nutbeam et al. (2018a) explained the following types of health
literacies: (a) functional literacy is a requirement to perform common daily activities
related to health in numeracy, reading, and writing, (b) interactive literacy is reasoning
and literacy capabilities needed to contribute to routine communication in health topics
and implement innovative information to alter conditions, and (c) critical literacy is
essential in analyzing and processing information in expressing self-efficacy to help
preserve life and to contribute to the well-being of society.
Rademakers and Heijmans (2018) stressed the importance of functional health
literacy and other elements such as understanding, cognitive capabilities, information
managing, behavior, emotional, and instinctive qualities. Functional health literacy
conveys a unique understanding of health risks, properly utilizes the health system, and
applies health-related knowledge to the necessary activities (Nutbeam et al., 2018a).
Understanding various health literacy classifications enables healthcare providers and

39
managers to differentiate needed strategies to improve low health literacy in prescriptions
devotion and behavioral modification to attain autonomy in health decisions (Nutbeam et
al., 2018a). Hickey et al. (2018) conducted a study to address the importance of
functional health literacy in older adults with comorbidities and economically challenged,
focusing on distinct ethnic populations. Additionally, Hickey et al. found substantial
variations in older populations, minorities, and individuals with English as a Second
Language in health literacy.
Global Highlights of Low Health Literacy
Increasing global health literacy intervention on healthcare utilization might
improve health outcomes and reduce healthcare costs. There is a proliferation of research
on low health literacy due to its detrimental effect on individuals’ overall healthcare
systems domestically and internationally. Trezona et al. (2018) believed that research had
provided reliable proof to identify low health literacy as a public health concern
worldwide. Trezona et al. added that health literacy is achievable through an operative
health education intervention and the enhancement of the health system. Furthermore,
Trezona et al. conducted a systematic exploration of several countries such as Australia,
Austria, China, New Zealand, Scotland, and the United Kingdom to present how they
incorporated health literacy goals and strategies into their health policies. These countries
emphasized specialized education to enhance interaction between health consumers and
the healthcare system to advance health literacy (Trezona et al., 2018).
The World Health Organization (WHO) recognized health literacy as a basis and
threat to health with initiatives to accomplish liberation and fairness through investment

40
in maintainable growth (WHO, 2017). Paakkari and Okan (2019) presented several
arguments on health literacy related to education: (a) health literacy is the result of
education, (b) health literacy is significant to the primary proficiencies of OECD, and (c)
the educational foundation should include health literacy. In a study involving the
correlation between adolescent health literacy level and household, sex, wealth,
selfassessed health in 12 European countries, the children in Finland and Macedonia
scored higher on health literacy level when compared to other children in the study
(Paakkari et al., 2020). Paakkari et al. (2020) established variations in health literacy
parallel among the participants in various socioeconomic positions. Additionally, the
authors confirmed the integration of health literacy education into the school curriculum
in Finland (Paakkari et al., 2020). This study and other numerous examples of the
positive impact of health literacy illustrate the achievement of adequate health literacy
with proper implementation in early childhood. Understanding health literacy facilitates a
plethora of knowledge to healthcare providers and policymakers in providing educational
resources for children, adolescents, and adult levels to meet the demands to improve
health outcomes.
Global health literacy promotion is evidence in many country’s health policies to
identify problems and interventions to increase health literacy. The implementation of the
Shanghai pronouncement fostering health in the 2030 sustainable development program
encompasses difference components involving health literacy to achieve a global
healthier society (Pleasant et al., 2020; WHO, 2017). Pleasant et al. (2020) recognized the
Shanghai declaration as the highlight of health literacy promotion in the global arena;
they mentioned several initiatives from other countries to address health literacy, the

41
vision for health literate Canada and the New Zealand health strategy 2016 to 2026,
strategic plan on health literacy should be used as a guide for Chinese citizens (Pleasant
et al., 2020). Recognizing educational departments and government policies in bringing
health literacy awareness is essential in the early stages of the development of health
literacy (WHO, 2017).
The economic burden of low health literacy, health inequality, poor quality of life,
and low healthcare utilization are concerns for personal and societal wellbeing globally.
Health literacy intervention has potential benefits for health and financial outcomes for
society and organizations. Stielke et al. (2019) reviewed numerous peer-reviewed
journals and confirmed a relationship between cost-efficiency and health literacy
mediation. Furthermore, Stielke et al. illustrated a return on investment and social return
on investment from a thriving health literacy program. Hashemi-Shahri et al. (2020)
warned that the COVID-19 global pandemic had presented misinformation, personal
confusion, and economic hardship to society. Health literacy intervention is essential to
enable individuals to make good health decisions (Hashemi-Shahri et al., 2020).
Health literacy is a global challenge that needs personal, community,
organizational, state, local, and international bodies’ involvement to educate the global
populations on health concerns. As globalization has created more movement and
interactions enabling the spread of outbreaks, improved health literacy becomes
imminent, as proven by the COVID-19 global pandemic disasters. Abdel-Latif (2020)
reported the Corona Virus pandemic as the significant difficulties the healthcare
organizations and policymakers have encountered in the 21 st century. The emphases of

42
this study are to understand how adequate health literacy can impact the US population in
health utilization and increase profitability for health insurance companies and reduced
expenses per patient.
The Influence of Low Health Literacy on Patient’s Health
Several studies and literature reviews have identified poor health literacy as an
influential determinant of good health that impacts different facets of wellbeing (Healthy
People 2030, n. d.; Michou et al., 2018; Pelikan et al., 2018; WHO, 2017). In these
studies findings, individuals experiencing poor health literacy have deprived health
behaviors and results, and exhibits low preventive care initiatives (Schillinger, 2021),
lacked knowledge on self-medical disorders, lacked self-efficacy managing conditions,
engaged in healthcare overutilization and underutilization in other cases, experienced a
lack of illness control, and more significant mortality and morbidity (Michou et al.,
2018). Schillinger (2021) identified that low health literacy interrupts effective
communication and understanding between healthcare professionals and patients.
MacLeod et al. (2017) study’s findings indicated that older patients with limited
health literacy (HL) supported other studies’ discoveries, adding that the poor HL is
prevalent in older populations with chronic conditions, particularly males, poor
education, and advanced comorbidities. MacLeod et al. maintained that low HL was
related to poor patient happiness, low adherence to preventive care, problems in the
national healthcare system, increased expenditures, and excess use. They projected a
continuous heightened economic impact as the population ages and pointed out the

43
implementation of adequate health literacy programs to remedy the problem (MacLeod et
al., 2017).
Svendsen et al. (2020) argued that people who exhibit adequate HL possess more
significant health knowledge than adversaries with limited health literacy. A similar study
involving youth and young adults battling end-stage kidney disease (ESKD) investigation
on the relationship between individuals with limited HL and sufficient HL level of
healthcare use confirmed an opposing view to other scholars that no significant variation
exists on the level of healthcare use, emergency department use, duration of
hospitalization, and avoidable hospitalization between patients with insufficient HL and
patients with sufficient HL (Levine et al., 2018). In addition, Levine et al. noted that a
higher level of healthcare utilization was related to a specific subgroup, identifying
insurance type and the marginalized population. A few of the presented studies illustrated
a significant gap in the disparities faced by the minority population in health literacy
level. Understanding an individual’s health literacy level is crucial in implementing
strategies to increase health literacy on medical utilization to reduce healthcare expenses.
Another set of researchers demonstrated the impact of a successful education
program on wide-ranging health literacy skills in developing health literacy to influence
behavioral health change in older adults (Uemura et al., 2018). Walters et al. (2020)
reported that health literacy mediation is efficient in behavioral health transformation.
Walters et al. detected the lack of patient-oriented results and mediations. Walters et al.
suggested that patients should participate in structuring the health literacy program
instead of instructing health consumers on how to make changes. The overall goal of

44
health knowledge education is to create health awareness for healthcare stakeholders to
implement change.
Medical/Healthcare Service Utilization
Identifying the numerous services and centers is essential in analyzing healthcare
utilization and groups responsible for higher healthcare costs. Centers for Medicare and
Medicaid Services (2017) described various categories of healthcare service utilizations
deliveries. The available delivery for patients is facilities, such as hospitals services,
ambulatory services, dental, home health, nursing, prescriptions, durable and nondurable
medical equipment (World Health Organization, 2017). According to Mitchell (2020), In
2017, the Medical Expenditure Panel Survey identified that the bottom 50% of the U.S.
population were classified to spend fewer dollars than the top 1% of the highest users of
healthcare services with average yearly spending over $115,000. Mitchell added that the
national healthcare higher spending concentration in the U. S. is within the 5%, 10%, and
30% of the population.
Medical utilization involves over and underutilization of medical services. Health
service over and underuse may result in higher healthcare costs and diseases due to the
lack of preventive care, creating monetary challenges for patients and health insurances
organizations. Schillinger (2021) observed that people with limited health literacy use
higher healthcare services. Gawron et al. (2021) affirmed that barriers to healthcare
utilization, such as poverty, race, ethnicity, and comorbidity encumbrance, separately
determine involvement in health screening. Goto et al. (2019) argued that environmental
conditions related to jobs obligation, access to a health provider, and living situations

45
were significant in participating in healthcare use. Health literacy and healthcare
modifications, including primary health screening, supports increased participation
(Gawron et al., 2021). Improving access to healthcare and primary care is essential to
obtaining routine check-ups to detect diseases early.
Healthcare utilization expenses can create privations for individuals suffering
from various diseases, especially cancer. Zheng et al. (2020a) conducted a study of cancer
patients’ survival to investigate the correlation between the financial difficulties related to
medical and nonmedical expenses involving medical utilization and selfevaluated health.
Zheng et al. found that patients with frequent emergence room visits, poor preventive
care, and low self-evaluation of health incurred increased medical and nonmedical
economic adversities. Zheng et al. (2020b) confirmed that the preceding studies align
with other studies findings that cancer patients have much higher overall medical and
nonmedical costs when compared to patients with other diseases. Health literacy
interventions might bring understanding in early health screening and disease detection to
reduce the further overall hardships related to health.
Overutilization is one of the prevalent factors for higher healthcare costs in the
United States. Berkowitz et al. (2018) stated that lessening elevated healthcare costs
associated with higher utilization is a shared objective of the health community. In
research related to healthcare consumption and spending, the authors confirmed that food
insecurity was one of the determinants of overutilization involving constant emergence
room services and inpatient stay (Berkowitz et al., 2018). Health literacy mediation is
crucial in understanding adequate healthcare utilization to reduce financial waste. Clark’s

46
et al. (2020) study showed that older people were prone to potentially inappropriate
medication (PIM), which was confirmed to amplify healthcare utilization and costs. The
consequences of high healthcare utilization are the increased costs to patients and health
insurance companies.
Various researchers have attributed higher healthcare utilization and expenditures
to an older population with different health needs in the U S. Research to understand the
healthcare utilization and economic costs of older individuals with a reduction in mobility
shows that as the number of older populations increases, so will utilization and costs
increase (Cheng et al., 2020). Although, Cheng et al. (2020) affirmed that gaps exist in
the financial burden connected to healthcare utilization of the older population,
particularly with reduced physical activities, and recommended less expensive
interventions to enhance wellbeing for people with this condition. These studies have
affirmed that healthcare managers must educate patients on adequate health utilization to
mitigate costs.
Chisolm et al. (2021) presented a paucity of studies to establish the relationship
between health literacy, health service utilization, and the transition speediness of youths
with exceptional healthcare necessities. Chisolm reported results varying with other
studies that there was a slight relationship between HL and transition readiness. Chisolm
et al. (2021) noted evidence that emergency department stays increase utilization, as was
established by various researchers investigating healthcare utilization and costs. This
study’s findings provided innovative awareness in the part health literacy plays on youth
transitioning from pediatrics to self-managed healthcare (Chisolm et al., 2021). In another

47
study, Goto et al. (2019) observed a disconfirming relationship between health literacy
and health service utilization, confirming that universal health insurance in Japan and
Taiwan might be a determinant of accessibility, affordability, and health service
utilization. Goto et al.’s further confirmed that frequent emergency department visits
resulted from existing medical conditions and obesity instead of health literacy. Goto et
al. argued high participation in employees’ annual voluntary preventive care was a factor
in medical services uses rather than health literacy. The importance of adequate HL was
proven to mitigate healthcare utilization and costs in other studies.
Estimating over-utilization of healthcare services is challenging due to various
factors in calculating excess utilization. Van Diepen’s et al. (2018) study categorized
variation in hospital utilization into low, medium, and high in investigating patients with
Non-ST-Segment Elevation Acute Coronary Syndrome (NSTE ASC) critical care unit
use. They found that the critical care unit contributes to approximately half of all hospital
costs, and the group of patients mentioned above has increased hospital consumption (van
Diepen et al., 2018). Another observation van Diepen et al. (2018) discussed was that
patients who adopted low utilization contributed to an estimated savings of more than
$100 million during the duration of the study and realized more than $18 million yearly
in reserve. In another research study on healthcare use in an underserved,
incomedisadvantaged community, Hargreaves et al. (2019) found that low utilization of
preventive healthcare service in patients with adverse childhood experiences could
contribute to deteriorating health standing. However, Hargreaves et al. confirmed, van
Diepen et al.’s findings that individuals with high comorbidity have greater healthcare use

48
and expenses. This study is significant in demonstrating the impact of interventions that
could reduce healthcare overutilization and costs.
Lack of healthcare access and health information leads to inadequate utilization.
Goto et al. (2019) proved that individuals with paid universal healthcare access have a
higher rate of sufficient medical utilization. In their study, to afford and obtain access to
care, employer initiation for routine care supported adequate healthcare use.
Overutilization of healthcare services leads to higher-than-expected healthcare costs for
health insurance companies and patients. Overall, health literacy interventions could help
patients understand the impact of healthcare utilization, under and over-utilization
involving hospitalization, emergency room visits, inpatient services, and other forms of
use. Although Goto et al. made an opposing discovery, they agreed that healthcare
intervention by access, affordability, and service increased healthcare use regardless of
health literacy. Engaging in adequate healthcare utilization is essential in detecting
treatable diseases early. Healthcare providers, managers, and researchers are the primary
educators supporting health literacy to reduce the nation’s health costs. Increasing health
outcomes through health literacy intervention is proven through research and
metaanalysis of past and current data.
Gap in Literature
A notable gap exists in understanding the impact of health literacy on healthcare
professionals in resisting vaccination. Although El-Elimat et al. (2021) identified various
factors responsible for vaccine hesitancy, mentioning transparency and established that
healthcare professionals provides the best dependable communication on COVID-19

49
vaccine. El-Elimat et al. did not explain why medical doctors, nurses, and other
welleducated individuals have refused to get their Covid-19 vaccine shots and boosters
amidst this current pandemic. Numerous other notable gaps exist in research on the
relationship between health literacy intervention, health outcomes, and health literacy
measurement scale. Okan et al. (2018) identified gaps in children and adolescents’ health
literacy research. To enhance the accuracy of the health literacy measurement scale, the
standardization of health literacy measuring instruments, particularly in children and
adolescents, is proposed (Okan et al., 2018). Similarly, Schillinger (2021) acknowledged
several health literacy research gaps associated with the reliability and validity of the
measuring tools to reduce bias and error. Furthermore, Schillinger pointed out that
research is eminent in minority populations with insufficient representation due to certain
beliefs as the population with the highest health inequality.
Additionally, Schillinger (2021) found that it is essential to expand and improve
HL studies to understand the perspectives of more researchers in this field. Using
descriptive research to include health disparity and multiple ethnic populations might aid
positive health outcomes (Schillinger, 2021). Crossley et al. (2020) observed the paucity
of research related to patients’ low HL and proposed a research focus to address
healthcare providers’ receptiveness to people in reducing limited health literacy.
Transition
The purpose of this qualitative, multiple case study was to explore the strategies
private health insurance managers use to increase patients' healthcare literacy on medical
utilization to reduce healthcare expenses. In Section 1 of this study, the major topics

50
addressed were the problem statement, purpose statement, nature of the study, research,
and interview questions. The inclusion of the conceptual framework, the health belief
model, forms a lens to view the research question and is essential to understand various
constructs crucial in making behavioral health change. The operational definitions of a
few terms include assumptions, limitations, and delimitations surrounding the study.
Conclusively, to review existing data on the study, I presented the analysis and synthesis
of the health belief model (HBM), the Andersen model, and several constructs, healthcare
costs, overview of the U.S. healthcare costs, and health literacy.
Section 2 included the expansion of the purpose statement, the explanation of the
role of the researcher and participant in a study. In addition, the research method and
design, population and sampling criteria, ethical research protocols, data collection
instruments and techniques, data organization techniques and analysis, and reliability and
validity were presented. In Section 3, I illustrated the findings, recommendations for
business, application to professional practice, reflection, and conclusion of the study.
Section 2: The Project
Data collection and use of semistructured interviews were primary methods for
this qualitative multiple case study to identify strategies private health insurance
managers use to reduce healthcare costs originating from medical utilization. In this
section, I reiterated the purpose statement, identified the researcher's role, and explained
the participant's selection procedures in the study. Additionally, I discussed the research
method and design, population and sampling, and ethical research protocol involved in
this study. Furthermore, I discussed the data retrieval instruments, techniques,

51
organization approach, and analysis to complete this study. Importantly, I also explored
the processes to achieve reliability, validity, and the summation of the project in this
section of the study.
Purpose Statement
The purpose of this qualitative, multiple case study was to explore the strategies
private health insurance managers use to increase patients' healthcare literacy on medical
utilization to reduce healthcare expenses. The targeted population consisted of private
health insurance managers from two health insurance companies in Nevada who have at
least 3 years of experience effectively improving patients' health literacy on medical
utilization to reduce healthcare expenses. The findings of this study may have a positive
social change in creating health-literate individuals for improving communities' citizens'
health and reducing patient healthcare expenses.
Role of the Researcher
The researcher is crucial in collecting relevant data to establish findings beneficial
to academics, institutions, and organizations. Therefore, the researcher must collect and
use data integrity to avoid biased and unethical research. The public perception of a
researcher, particularly at the doctoral level, is highly regarded as knowledgeable, and
this thought influences my commitment as a researcher to achieve quality research.
Geddis-Regan et al. (2021) described a researcher as a data collection instrument, analyst
of data, and knowledgeable source in answering questions related to the researcher's role.
My role as a research instrument was to search, document, analyze, interpret, and present
findings from interviews and archived records to my academic institution and beyond.

52
I have over 10 years of working experience in healthcare organizations, billing,
coding, and processing medical claims from various health insurances. The knowledge
acquired from the job facilitated my comprehension of critical concepts on strategies to
increase health literacy on medical utilization to reduce healthcare costs. Notwithstanding
my affiliation with the healthcare industry dealing with medical billing and seeing
firsthand the impact of healthcare costs on individuals, private, and public insurance, it is
paramount that I present credible findings free of bias. Hammersley and Atkinson (2019)
posit that participant and researcher rapport is crucial in conducting quality research. A
researcher engages several empirical case design studies to retrieve information through
semistructured interviews and analysis of firm documents (Yin, 2018). I did not have any
prior or existing relationships with the participants for my interviews. As the research
instrument, my role entails avoiding certain biases that might challenge my findings
credibility.
The role of a researcher concerning ethics in following the research process is
vital to achieving ethically grounded research. Saunders et al. (2019) identified the
integrity and objectivity concerning the researcher, respect for others, non-maleficence,
confidentiality, and maintaining safety. The Belmont Report specified three guiding
principles in conducting ethically acceptable research: justice, respect for persons, and
maleficence (National Commission for the Protection of Human Subjects of Biomedical
and Behavioral Research, 1979). As a researcher, I was obligated to adhere to the Belmont
Report principles of respect for persons by treating each of my participants as an
autonomous representative and providing the necessary information regarding informed

53
consent. I ensured beneficence by maximizing research benefit, reducing risks to the
participant, and expressing justice by treating the participant justly throughout the
interaction. Furthermore, I retrieved data by following the University's ethical standards
and the Belmont Report’s ethical research principles, including human subjects. I ensured
that I received informed consent from all the participants, protected their privacy and
confidentiality, and provide access to data if requested.
Saunders et al. (2019) recognized three kinds of bias in conducting semistructured
interviews: (a) interviewers bias, non-verbal conduct influencing the participant’s answer;
(b) response bias, participant sensitivity related to being interviewed; (c) participation
bias, originated from a person or firm’s individualities. I mitigated researcher bias by
including all the data collected from semistructured interviews in my transcription and
interpretation. To avoid participants’ sensitivity towards the interviewer, I conducted my
behavior, including facial expression, to allow the participant to answer interview
questions freely. Johnson et al. (2020) proposed that researchers illustrate credibility by
presenting honesty and transparency in acknowledging bias during the research process.
Fusch et al. (2018) found that a researcher can lessen bias by selecting of appropriate data
collection techniques applicable for the study. To maintain research objectivity includes:
(a) collecting data using the proper method and (b) avoiding the three types of bias
identified to support the validity and credibility of this study.
Mitigating bias is part of the researcher’s role and involves methods for presenting
the inquiry, ascertaining rapport, and clarifying answers (Bergen & Labonté, 2020). I
reduced bias through asking questions and adherence to the Walden IRB principles of

54
research ethics. Mallon and Elliott (2019) studied novice and experienced researchers
who acknowledged facing convoluted personal and professional sentiments regarding
their work. Fusch et al. (2018) found that information from a personal lens is a few of the
main difficulties’ novice researchers face when conducting qualitative research due to the
conventions of new researchers regarding lack of bias in data collection. As unnatural as
removing bias, I strived to lessen the researcher's bias, and avoided a personal perspective
or dispositional influence during data collection and interpretation. Yin (2018)
recommended applying member checking or transcript validation to prevent
misconceptions and individual opinions in mitigating bias. I conducted a follow-up
interview with the participants for member checking of transcript interpretation to
confirm the accuracy of data prior to the interpretation of findings. Although
unforeseeable circumstances could present challenges in the interviewing process, I
accomplished my data collection goal through proposal completion with the Walden IRB
approval number required for doctoral students.
Saunders et al. (2019) postulated that an in-depth interview allows a researcher a
chance to explore findings through the five P's: "prior planning prevents poor
performance" (p. 401). Yeong et al. (2018) identified a dependable interview protocol as
critical to collecting excellent interview data. I abide by the interview protocol (Appendix
A) for my study in interviewing participants. Yin (2018) recognized several typical case
study interview protocols: (a) the overview of the study, (b) data collection procedures,
(c) protocol questions, and (d) a brief outline for the study report. The interview protocol
was a guide to maintaining consistency and direction. I shared the interview protocol
prior to starting the interview and followed the protocol by presenting the questions in an

55
orderly list. I recorded the interviews, took notes, and collected relevant participant data
for interpretation of findings. Adherence to interview protocols ensured that I collected
relevant primary data to explore strategies managers use to increase health literacy on
medical utilization and a reduction of costs.
Participants
The eligibility criteria for this study required the participants to consist of private
health insurance managers from two health insurance organizations in Nevada who have
at least 3 years of experience effectively improving patients' health literacy on medical
utilization to reduce healthcare expenses. I used a purposive method through email and
telephone calls to reach selected participants who possess over 3 years of experience
working on programs to increase patient health literacy and understand medical
utilization. I emailed the study invitation letter (Appendix B) to the potential participants,
which details the aim of the study, the voluntary, and unpaid nature of participation.
Saunders et al. (2019) identified that a researcher is significant in selecting eligible
participant based on the study concentration to address the research and interview
questions. Forero et al. (2018) argued that using different purposive sampling approaches
allows for an opportunity to achieve variation in proficiencies and the understanding to
boost the credibility of the study outcomes. Furthermore, the purposive sampling of three
participants from two organizations allowed me to collect quality data and address my
research and interview questions.
I interviewed three private health insurance managers known for achieving
effective strategies to increase health literacy on medical utilization to reduce expenses in

56
Nevada. Moser and Korstjens (2018) posited that the sampling strategy is acceptable
when the purposive sample and location chosen advance knowledge to the topic of the
study. The sample consisted of three private health insurance managers from two
organizations in Nevada responsible for strategies to increase health literacy on medical
utilization to reduce costs. When Institutional Review Board (IRB) granted permission to
conduct an interview, I proceeded with seeking access to participants through my
personal network to conduct qualitative interviews. McGrath et al. (2019) identified
qualitative interviews as the possibility of extracting deeper information particular to
participants, understanding various exceptional occurrences and observations.
Forecasting participants’ sampling strategies in qualitative research involve the number
of observations, interviews, focus group interactions required to ascertain if those
outcomes will parallel rich data (Moser & Korstjens, 2018). I proceeded with the
planning of collecting organizational information to locate a purposeful sample for initial
contact.
Alexander and Smith (2019) identified the importance of administrative access as
key to qualitative research. Among many strategies to permit access to participants
identified by Saunders et al. (2019), ascertaining credibility, applying appropriate
language, and pinpointing potential strengths to the organization were a few of the
essentials in receiving acceptance. I established credibility as a Walden University
doctoral student researching my doctoral study to explore the strategies to increase health
literacy on medical utilization to reduce healthcare expenses. Additionally, I presented the
participants with a well-crafted email using suitable languages highlighting that the
participant's collected data and privacy remains confidential. I gained access to the

57
participants through my personal network by identifying the leading company in health
interventions. A researcher might offer an organization vital information to compromise
for access through a study of concern within ethical principles (Alexander & Smith,
2019). I might offer to present potential anticipated study’s outcome benefits to
participants or organization to facilitate access if necessary.
Abadie et al. (2021) proposed that many scholars have presented that building
trust is a social development that enables the researcher and participant to comprehend
both individual’s purpose and exchange shared goods. Building rapport with participants
through telephone conversations, email, and visits to the organization are approaches to
institute an influential association. McGrath et al. (2019) stated that the foundation to
establishing rapport is a sense of closeness. Additionally, rapport is vital when
interviewing to allow the participant to offer a rich and comprehensive encounter with the
phenomenon (McGrath et al., 2019). I started a conversation with the potential
participants concerning the research topic to build a rapport, and asked some polite
questions on the participant’s interest, and expressed appreciation for volunteering to
grant an interview. A feel of rapport and, in some cases, an opportunity to interact with a
researcher was essential to the respondent (Heath et al., 2018).
Research Method and Design
Basias and Pollalis (2018) postulated that research incorporates an innovative
study following a methodical approach to enhance understanding to institute or approve
data, mitigate issues, create innovative theories and solutions to problems. The
methodology and design for my study were qualitative with a multiple case study to

58
explore the strategies private health insurance managers use to increase patients'
healthcare literacy on medical utilization to reduce healthcare expenses. The research
method and design enabled me to access in-depth information to answer my research
question and understand issues and potential solutions to health literacy. The following
subsections are the detailed explanations of the research method and design relevant to
retrieve information for my study.
Research Method
The decision to use the qualitative research method was to share an interactive
experience with my participants to understand the strategies private health insurance
managers use to increase patients' healthcare literacy on medical utilization to reduce
healthcare expenses. I selected the qualitative method to interview, take notes, and
analyze firms document to find answers in my exploration of my research question. Kim
et al. (2017) addressed the importance of the practicality of qualitative method in
achieving camaraderie and efficacy in acquiring rich data in gaining thoughtful replies
and information. Using a qualitative method enabled me to interact with the participants
and gained deeper insight into the concept of healthcare literacy. The findings from this
qualitative research might provide individuals: (a) with adequate health literacy
knowledge, (b) promote healthy well-being for life, and (c) reduce healthcare costs for
patients, private insurance providers, and public health funding agencies. The qualitative
method enabled me to use member checking from a small sample of knowledgeable and
experienced individuals from two organizations to answer flexible research and interview
questions to obtain relevant knowledge of the phenomenon for the study.

59
Gephart (2018) described qualitative organizational research as a numerous
approach procedure engaging qualitative evidence involving linguistic codes and stories,
spoken communication, and transcribed scripts to comprehend organizational practices. A
researcher uses a qualitative method to answer questions and highlights outcomes to
rationalize how and why a conclusion was reached (Holtrop et al., 2018). The preceding
explanations and justifications were vital to selecting the qualitative method as an
alternative match to address the research aim for the study. The qualitative method allows
a researcher to collect unique information from an organization to interpret the study
findings through an in-depth analysis to academia and the public.
The quantitative study includes the orderly and experimental examination of a
phenomenon from a statistical and measurable approach analyzing numerical information
to provide the primary relationships between observation and arithmetic illustration
(Basias & Pollalis, 2018). A quantitative researcher retrieves numerical data with a
homogenous questionnaire, controls variables, and the setting of the study (Rutberg &
Bouikidis., 2018). Computing and comparing relationships using mathematical figures is
not the emphasis of my research; therefore, I will not be using the quantitative research
method; the quantitative method is a mismatch to the research objectives. Furthermore,
Basias and Pollalis (2018) explained a mixed methodology to include qualitative methods
to explore and interpret and quantitative methods to study phenomena using statistical
assessment was not needed for my study. Depending on this research aim, I only needed
to analyze and decode the strategies health insurance firms use to increase patient literacy
on medical utilization to reduce healthcare expenses. The research question lacked
variables to measure and compare the numerical data statistically, so the mixed method

60
disqualifies as the selected method for this study. Although Creswell and Hirose (2019)
maintained that the integration of the mixed method provides further understanding, I did
not use the mixed method for this study. The suitable method to address the open-ended
research interview questions was my qualitative method.
Research Design
There are various qualitative research designs: phenomenological, ethnographic,
narrative, and case study. The phenomenological design focuses on discovering an
individual's insight and lived experience to understand the phenomenon in the study
(Ataro, 2020). I was not seeking an individual’s lived experience of a phenomenon but
rather an organizational strategy on a concept; therefore, a phenomenological design was
not appropriate for this study. Ethnographic design is another design a qualitative
researcher can use to understand the cultural perspectives of an individual or group.
Ethnographic refers to learning about people from their experiences in historical and
cultural contexts by immersion in the population and actively engaging with the
participants (Jones & Smith, 2017). This study lacked the criteria to meet the
requirements to perform an ethnographic study due to the absence of cultural groups. I
did not use an ethnographic design for this study. Halkias and Neubert (2020) posited that
a narrative design is similar to a phenomenological study exploring identity,
understanding experience, and personal and social formed meaning on a particular
concept. Narrative design involves telling a personal story of an individual s life account,
which is not the intention for the participants to tell a personal narrative. I did not use a
narrative design to explore the study phenomenon.

61
The case study design was the best option to understand and answer my research
question on the strategies private health insurance companies use to increase medical
utilization and reduce healthcare expenses. Scholars might use case studies for specific
unfamiliar or under-assessed phenomena for limited or scarce empirical evidence of
subsets of data (Çakar & Aykol, 2021). I used a case study to address the limited
information on health literacy in healthcare organizations. Yin (2018) explained a case
study as an empirical method that investigates a contemporary phenomenon in depth and
within its real-world context, especially when the boundaries between phenomenon and
context may not be evident. A case study design includes two alternatives, single-case and
multiple-case studies (Gustafsson, 2017). Yin (2018) added that the choice of a case
depends on the theoretical disposition of the study and whether or not you are using
participants from multiple locations or more than one location.
A single-case study is an adequate strategy based on these five single-case
justifications: analytical, rare, usual, revelatory, and longitudinal case (Yin, 2018).
Although, Hoorani et al. (2019) proposed that a single case study consists of one case.
Therefore, a single case study is relevant for the concept of the study, but I did not use it.
A researcher acknowledges that multiple case study ensures the exploration of more than
one observation within and outside cases (Halkias & Neubert, 2020; Yin, 2018). Halkias
and Neubert (2020) stated that a multiple case study ensures a deeper and holistic
understanding of real-life events. A multiple case study enabled me to collect enough
information and required no new information over a single case study to ensure data
saturation. I chose the multiple-case study design to gain more information on the

62
research topic and interview questions. Additionally, the multiple case study enabled me
to develop a comparable or an opposing perspective from the two selected organizations
on health insurance managers’ strategies to increase health literacy on medical utilization
to reduce healthcare expenses.
Lowe et al. (2018) indicated that a significant concept of qualitative research is
data saturation. A researcher ensures data saturation by collecting data until no new
information, codes, or themes emerges. Lowe et al. added that data saturation occurs
when additional data is insignificant to explore extra information important to the
research phenomenon. Part of guaranteeing data saturation for this study involved
interview transcripts, a member checking process, and data analysis to generate relevant
themes for interpretation of the findings. I interviewed participants and probed for further
information until no more or no new information arise. I also analyzed the interview
transcripts until no new codes and themes emerged. To validate the interview transcripts,
I followed up with participants through the member checking process to confirm the
accuracy of the interview data.
Population and Sampling
I selected participants for this study using population sampling. The study
population consisted of private health insurance managers from two health insurance
organizations in Nevada who have at least 3 years of experience effectively improving
patients’ health literacy on medical utilization to reduce healthcare expenses. Lu and
Franklin (2018) identified population study, random sampling, and convenience sampling
as the three methods of choosing participants that investigators might practice when

63
conducting research. Lu and Franklin recognized population sampling as the “gold
standard” with generalizability challenges essential to narrow the targeted population
using purposive sampling. Sampling is vital in a study with a sizeable and physically
isolated population; therefore, a researcher must devise a probability or non-probability
sampling (Lu & Franklin, 2018; Tyrer & Heyman, 2016). Tyrer and Heyman (2016)
advised that a sampling technique involves rigor to guarantee minor fault and bias and
improve representation.
The two methods of population sampling encompass: (a) probabilistic sampling
which, identified as the subjective decision of the investigator, and (b) nonprobability
sampling involves numerous categories: purposeful, convenience, snowballing, and quota
(Berndt, 2020; Bhardwaj, 2019; Elfil & Negida, 2017; O'Sullivan et al.,
2016). Purposeful sampling is the appropriate strategy a researcher applies in choosing
qualified participants to answer the research question (Elfil & Negida, 2017; Marshall,
1996; Tyrer & Heyman, 2016). The main criteria for choosing research participants
depends on the participants’ knowledge and experience, voluntary participation, and
compelling and articulated communication on the concept being discussed. Purposeful
sampling was appropriate in selecting participants in this study to address the research
and interview questions because the participants possess the intellectual ability to
contribute to the primary data. I used purposive sampling to choose three managers from
two organizations (one from one organization and two from the other organization) in
Nevada to answer the research interview questions in the multiple case study.

64
The convenience sample includes using the most available participants to create
high-quality data, and intellectual trustworthiness of research (Elfil & Negida, 2017;
Marshall, 1996). I did not use convenience sampling because I was not seeking the most
accessible participant. Snowballing sampling involves using current respondents to
identify familiar future participants in difficulties recruiting respondents (Etikan et al.,
2016). I did not experience challenges locating respondents; therefore, snowballing
sampling was inappropriate for the study. Quota sampling depends on selecting
participants with common attributes of the population without having prior knowledge of
an individual’s demography (Lamm & Lamm, 2019). Quota sampling was not adequate
for this study because I was not exploring the differences in subgroups.
Data saturation is when there is no new insight contributed to the body of the
research, indicating that the researcher had reached the maximum informational
redundancy (Alam, 2020; Saunders et al., 2019; Varpio et al., 2017). Constantinou et al.
(2017) added that for a researcher to explore a phenomenon comprehensively to represent
reality, transferability, confirmability, and dependability that a plethora of data are
necessary. Consequently, data saturation demonstrates adequate data retrieval to explain
the study and a standard that meets qualitative study's ontological and epistemological
groundwork (Constantinou et al., 2017). Boddy (2016) suggested that the sample size
selection is circumstantial in a qualitative study and partly based on the methodical
paradigm directing the study. I reached data saturation with a sample size of three
participants.

65
Multiple case studies involving more than two sample sizes contribute deeper
information to the research to achieve data saturation than a single case study (Yin,
2018). Additionally, Boddy (2016) included samples encompassing a single case that
provides essential and informative data but fails to reach data saturation. In this study, I
used multiple case study to retrieve data through interviewing three participants. The
sample size of three participants selected for this multiple case study to explore my
interview questions produced sufficient information to reach data saturation. The
triangulation of data using interviews, field notes, and the participant’s documents
facilitated data saturation for this study.
Member checking and triangulation is another alternative to achieve data
saturation. Lincoln and Guba (1986) explained member checking as participants’
commitment in informally checking the research data to improve the credibility of
information. Moon (2019) described triangulation as various approaches to collecting
manifold data through archival documents, researchers, and theories to reach data
saturation. Candela (2019) agreed that triangulation through member checking of data is
part of achieving data saturation. I interviewed three participants and utilized multiple
sources of data collection to triangulate to reach data saturation for this study to achieve
the study objective of exploring strategies private health insurance managers use to
improve health literacy on medical utilization to reduce healthcare costs, I used a
population sample of nonprobability sampling involving a purposeful strategy of three
participants from two health insurance organizations.

66
Ethical Research
Saunders et al. (2019) recognized the occurrence of ethical interests in research
during planning, designing, requesting access to organizations and participants, and data
collection, analysis, management, and reporting of findings. Scherzinger and Bobbert
(2017) identified the research Independent Review Boards (IRBs) as the body that
monitors research related to the safeguard of human subject participants in evaluating the
risk-benefit level and the proper documentation focused on the anticipated participants. I
started the data collection process when the ethics research committee ascertains various
elements of the research proposal with the Walden IRB approval number 05-05-22-
0982400.
Achieving informed consent to reach ethics standards, researchers must send
consent information with: (a) the aim and nature of the study, (b) duration, (c) declaration
of voluntary participation, (d) how to ensure data storage and the length of data storage,
and (e) privacy (Manti & Licari, 2018). When participation was confirmed, I presented an
informed consent form (Appendix C) to participants to sign and verbally explain in detail
the propositions of participation specifying the right to accept, reject and withdraw from
the study. Dankar et al. (2019) identified that respect for a person demands the self-rule of
every person participating in a human research study. Furthermore, I respected
participants’ autonomy by considering choices made during the interview about respect
for each person. I informed the participants that participating in the study is strictly
voluntary, and there is no offer of incentives.
Fernandez (2020) proposed that the researcher anticipate the participant’s
withdrawal, accept the request exclusive of penalty, and present informed consent to grant

67
understanding to minimize withdrawal requests. Additionally, the participants can
withdraw from the study, free from consequences, as participation was voluntary. The
withdrawal process involves letting me know the desire to withdraw through a formal
email or stating the intention during the interviewing process; then, I must acknowledge
the request to withdraw the participant from the study without asking for reasons. To
complete the withdrawal process, I would remove the participant and the collected
information from the study. Fisher et al. (2018) confirmed that a researcher should seek
information on what participants desire the most, a financial incentive, a significant
influencer for healthy research participation. To align with the ethical standards of
voluntary and withdrawal rights, I did not offer any compensation or incentive; rather, the
participant may receive a copy of the final study on request.
The Walden University (IRB) grants doctoral research students’ confirmation in
adherence to ethical values to proceed with data collection. The IRB’s documentation
guidelines concerning participants, data, and informed consent forms serve as a part of
the human criteria a researcher must adhere to achieve ethical research (Scherzinger &
Bobbert, 2017). I complied with the IRB’s procedures, pledging for ethical research by
following the Walden research ethics committee's various processes to achieve the review
and approval before selecting participants. I placed my approved Walden identification
number in my study after receiving approval from the IRB.
The National Commission for Protection of Human Subjects of Biomedical and
Behavioral Research (1979) established the Belmont Report's research protocol to
identify three directing principles: respect for life, beneficence, and justice. I abided by

68
justice, respect for persons, and beneficence to conduct an ethical interview by: (a) being
fair to participants, (b) protection for the participant, and (c) adherence to privacy. I
ensured that I received approval from IRB prior to proceeding with data collection. I
initiated the first contact through a request letter emailed to my targeted participants to
express the study's intention and wait for feedback. I also presented the informed consent
form to participants seeking understanding prior to each of them agreeing to participate in
the research. The participant was obligated to answer with an email with the word, “I
consent.” Manti and Licari (2018) declared that participants must be given and
understood research-associated information to accept or reject participation willingly.
The participant's privacy, anonymity, and confidentiality of data are paramount to
a researcher and the research ethics committee. Saunders et al. (2019) stated that since
research intends to answer questions related to a phenomenon, not related to the
participant answering questions. A researcher must guarantee privacy, anonymity, and
confidentiality in data analysis and writing of findings (Saunders et al., 2019). I
concealed the identity of my participants with pseudonyms and coded alphabetically
rather than use their actual names in adherence to anonymity in ethical principles.
Affirming the confidentiality of the research to participants, a researcher may obtain rich
data because of participants guarantee of these safeguards (Lancaster, 2017). To conform
with the ethical standards, I protected the collected information for this study, including
consent forms, recorded data, transcripts, and other documentation on a hard drive, and
will destroy the data at the lapse of 5 years. Before initiating the research proposal, I
contemplated my safety and the risks to contributors and ways to avoid harm to
participants by upholding the privacy of individuals and the data collected in this study.

69
Data Collection Instruments
In this qualitative research using multiple case study, I was the primary data
collection instrument. Johnson et al. (2020) and McGrath et al. (2019) suggested that the
researcher symbolizes the primary tool for gathering data. In this study, I collected data
through semistructured interviews using eight open-ended questions. Interviews were an
effective and credible qualitative data collection tool for learning a phenomenon by
exploring the experiences of a population (Muthanna, 2019). Muthanna (2019) indicated
that researchers utilize semistructured interviews involving questions to request enough
information to answer the phenomenal quest for the study. Iyamu (2018) recognized that
the face-to-face interview method increases data collection, probes answers, observes
verbal cues, and receives detailed information from participants' experiences. I
incorporated probing questions to obtain more information to enrich the data collection.
The interview protocol required me to present detailed interview questions for
data collection. Iyamu (2018) proposed that data collection follows five directing
ideologies: research ethics, interview protocol, pilot interview, choosing participants, and
demographic of respondents to enhance reliability, validity, and originality of
information. Yeong et al. (2018) argued that a researcher collects valid qualitative data
using a consistent interview protocol. The data collection process that applies to this
study: (a) interview protocol consisting of eight open-ended questions, as shown in
Appendix A, (b) probing follow-up questions, (c) and member checking method to direct
conversations. A researcher must implement data collection protocols through locating
participants, gaining access, and collecting data (Saunders et al., 2019). Yin (2018) noted

70
that case study data collection follows standard protocol; although, a researcher faces
uncertainty in collecting answers relevant to interview questions. I engaged with the
participants through virtual interviews using eight listed open-ended questions guided by
the interview protocol. Additionally, I reviewed publicly available documents relevant to
my research phenomenon, including participant’s flyer on health literacy programs that
experienced managers of private health insurance companies use with their patients.
Saunders et al. (2019) indicated that a researcher uses probing questions to
explore additional answers meaningful to the phenomenon. Kross and Giust (2019)
clarified probing questions as a subsidiary question focusing on the particular elements of
the original question. I used probing questions to extend conversations to refine and
collect meaningful answers to the research topic. A significant concept of research
triangulation involves participants in member checking (Candela, 2019). I included a
member checking process to validate interview transcripts by participant feedback to
confirm data accuracy. According to Saunders et al. (2019), before presenting the
recording device to the interview, the participant would have the information and reasons
why tape recording was necessary to support and enrich data interpretation, coding, and
transcription in its originality. I explained to participants that a researcher uses a
recording device as part of a data collection instrument, enabled detailed understanding,
and analysis of data during the interviewing process.
The trustworthiness of data conveys the validity and reliability of qualitative
research using the relevant model fitted for the study purpose (Rose & Johnson, 2020).
Rose and Johnson (2020) described validity as the exactness of answers and reliability as

71
the consistency of the research method selected and how a researcher pragmatically
expressed the approaches utilized in the study. A qualitative researcher can introduce
trustworthiness through credibility, dependability, confirmability, and transferability of
research findings (DeJonckheere & Vaughn, 2019, Guba & Lincoln, 1985; Lemon &
Hayes, 2020). I triangulated data, such as interview transcripts, field notes, and
participant program flyer, to confirm the trustworthiness of data in identifying strategies
to increase health literacy on medical utilization to decrease healthcare costs.
Triangulation consisted of using two or more data sources and methodology to verify the
trustworthiness of study data, analysis, and interpretation (Saunders et al., 2019).
Braun and Clarke (2021) stated that data sufficiency or saturation is vital to the
trustworthiness of qualitative research. To maintain the accuracy of findings and
uniformity of research methodology, I confirmed data accuracy through member
checking with the participant confirmation to reach data saturation. Furthermore,
improving the validity of this study ensured that I interpreted and presented the accuracy
of data with the help of the recorded data. Moser and Korstjens (2018) identified data
saturation as the end of data analysis and attaining sufficient data on the topic. I ensured
data saturation through member checking and triangulation by adding data from the
organizational archival documents and booklets related to the topic from other sources to
improve the trustworthiness of this study.
Data Collection Technique
The initial step to data collection was receiving approval from the university
ethics committee to proceed with data retrieval after ascertaining that a student has met

72
and understands ethical values concerning the human subject. Young et al. (2018)
indicated that data collection techniques have numerous approaches, such as telephone,
virtual, and face-to-face interviews. A face-to-face interview allows a researcher to gain
insight into the participant's physical body expression when addressing research questions
(DeJonckheere & Vaughn, 2019). A face-to-face interview will enable a natural
interaction between the researcher and the participants in response to each question,
ensuring that the participant expresses knowledge relevant to interpreting findings (Löhr
et al., 2020). Due the global COVID-19 pandemic, I utilized semistructured interviews
involving Zoom videoconferencing with participants to present eight open-ended and
follow-up probing questions to collect data. I also collected data through participant’s
program flyer related to the topic. During the interviews process, I used field notes and a
recording device to collect data for accurate analysis and findings interpretation.
DeJonckheere and Vaughn (2019) recommended giving informed consent to participants
on audio recording for data collection and allowing the participant to decide. Philippi and
Lauderdale (2018) stipulated that field notes significance in collecting interview and
organizational data aids in yielding copious, richly descriptive, helpful contextual
information useful to research.
DeJonckheere and Vaughn (2019) stated that semistructured interviews are
flexible, iterative, information gathering, insightful, and the critical source of information
for a qualitative researcher. McGrath et al. (2019) suggested that interviews should not be
casual conversation; instead, interviews are data collection mechanisms used to access
answers to several research questions. Following the interview protocol (Appendix A), I
enhanced the semistructured interview’s credibility and asked questions to maintain

73
consistency. I used the following interview protocol to guide the collection of data: (a) I
contacted the participant to reconfirm time and location, (b) a brief introduction of the
study, (c) presents an informed consent form already emailed to the participant. (d)
explained the duration and recording nature of the interview and confirmed the recording
agreement. (e) started the interview following the interview protocol, (f) I then thanked
the participants and gave information on member checking for a follow-up interview.
Data collection techniques through semistructured interviews were comprised of
both strengths and weaknesses. The strength of using semistructured interviews is that it
enables a researcher to use many open-ended questions and probe answers, elaborate, or
develop more answers (Saunders et al., 2019). On the contrary, semistructured face-toface
interviews hold several challenges concerning time, cost, and participants’ ability to
communicate that might be unpredictable. Another challenge was the anticipated
concerns of the researcher’s skill to collect valuable data to answer questions. Roberts
(2020) acknowledged that a researcher’s ability and the relevance of interview questions
presented determines the worth of the data retrieved during an interview. Considering the
advantages and disadvantages of semistructured interviews, I anticipated conducting a
quality interview to collect credible and reliable data. I projected that the duration of the
semistructured face-to-face interviews involving three participants from two
organizations would last 45 to 60 minutes each.
To conduct a pilot study helps researchers understand the due process of
interviewing protocol before commencing data collection. Lowe (2019) indicated that a
pilot study is to assess the data collection techniques and tools for excellence and

74
relevance. In a prior experience similar to a pilot study, I conducted for a class
assignment with two participants, presented research expectations, and dealt with areas of
strength and weaknesses in interacting with participants. Young et al. (2018) explained
that conducting a pilot interview is significant in data collection to ascertain sufficient
relevant data for transcription to explore the concept.
Birt et al. (2016) described member checking as encompassing a variety of actions
involving the validation of interview transcript through an uninterrupted readthrough and
approval by the participants to mitigate bias. Candela (2019) posits that member checking
is when a researcher presents data to the participant to review for correctness. To ensure
the accuracy of the information the participant provided, I conducted a follow-up
interview with the participant to make relevant changes. A few days after conducting the
interview, I returned the interview transcript summary to participants for verification of
data interpretation to confirm the accuracy of information after a few days to enhance the
credibility and validity of data.
Data Organization Technique
Various processes are relevant to organizing the raw data collected during the
interview with participants and the secondary data from other sources. Data organization
techniques are meaning a researcher uses to differentiate among raw data retrieved from
participants and the researcher’s explanation of data (Yin, 2018). I used an Evernote
recording pen and other recording devices to take notes and captured interview audio for
data coding, NVivo for transcription, coding, and thematic analysis. Maher et al. (2018)
stipulated that NVivo provides applicable data management and reclaimed storage for

75
analysis and write-up. I stored and managed my interview data with NVivo data analysis
and interpretation. Van Wyk et al. (2020) found that the management of research data
offers accessible admittance to data and involves (a) saving data, (b) adding metadata, (c)
backing up, (d) securing of data, and giving access to co-researchers. I organized, filed,
saved, backed up, and adequately labeled each interview from an individual participant
with pseudonym P1, P2, and P3 including date, time, year, field notes, informed consent,
and organizational documents for easy retrieval. Effective data management and
organization and their analysis are requirements for writing research reports and
distribution of study (Maher et al., 2018). I used data storage management software, such
as EndNote, NVivo, and Zotero, to save and manage data for easy access.
Maher et al. (2018) identified the eminence of rich and significant interaction with
data and noted that data documentation, management, and organization offers a
translucent audit trail. In this study, I documented the participant's consent form and
archival information from the organization to necessitate proper storage through a
personal safe to protect participant and organizational confidentiality. I have stored all the
data on my personal computer protected with a password lock exclusive to me. After
5years, all data related to the participants, as required by the IRB, will be electronically
deleted and shredded.
Data Analysis
Miles and Huberman (1994) proposed analyzing data collected from a case study
by reasonably connecting information to a planning sequence and constructing the
impending data. I analyzed participants responses by coding and rearranging codes to

76
create themes for study result. Lester et al. (2020) proposed that interpreting data analysis
in segments holds significance in the clarity of the method used for the researcher and
readers of the research findings. Lester et al. (2020) described several stages of data
analysis: (a) planning and categorizing data, (b) transcribing the information, (c)
understanding the data size, (d) memoing the information, (e) coding the documents, (f)
creating group and themes from the normal coded path, and (g) making the analysis
procedure apparent. I initiated the first data analysis stage to become familiar with the
recorded data by listening, transcribing, and understanding the raw data for precise
analysis. Using all of the strategies Lester et al. (2020) presented was vital to practical
data analysis of the study data.
After collecting primary data from participants through semistructured interviews,
data analysis followed to understand the information collected, transcription, coding of
data, and the interpretation of the findings. Lester et al. (2020) described the thematic
analysis as the presentation of codes, elaboration of groups, and finally, the construction
of themes. I applied thematic analysis. Varpio et al. (2019) specified that an inductive
thematic analysis method involving grounded concepts originates themes from the
investigator's data. I used the thematic data analysis to concisely present the raw data to
other researchers' comprehension. Kiger and Varpio (2020) proposed six conventional
frameworks for conducting a thematic analysis of data: acquainting self with the data,
producing preliminary codes, seeking themes, revising themes, describing, and
identifying themes, and generating reports. In analyzing qualitative interview data, a
researcher can use a computer-assisted instrument known as NVivo software, which is a
data analysis program to analyze the recorded interview data (Alam, 2020). I analyzed the

77
primary interview data using NVivo 12 to form codes and themes from the interview
transcripts.
Denzin (1978) mentioned four categories of triangulation: data, investigator,
theoretical, and methodological triangulation; a researcher can implement to view
research questions from various data sources and viewpoints. Methodological
triangulation uses numerous approaches, such as field notes, observation, and interviews,
to collect comprehensive and relevant data (Abdalla et al., 2018; Fusch et al., 2018). I
used methodological triangulation, which involves using data from my interviews and my
field notes, participant’s program flyer, and other sources for an in-depth understanding
of the topic to obtain themes for the study report. Methodological triangulation enabled
the parallel of interview data, participant’s flyer, review of literature data, conceptual
framework, field journal notes, and observations in gathering data for the final study
(Fusch et al., 2018).
Saunders et al. (2019) posited that thematic analysis combines connected data
drawn from various transcripts and notes and classifies key themes or patterns from
documentation for further consideration. During the coding process, which Williams and
Moser (2019) determined plays a vital role classifying data to identify themes. Williams
and Moser added that the coding process must be defined, rigorous, and constantly
applied to correspond validity and reliability customary to qualitative research. I
integrated my journal field notes, interview transcript, conceptual framework, and
literature about the phenomenon to form themes. After coding, I identified several key
themes related to my research questions, and the conceptual framework and incorporated

78
them to analyze study’s findings. The research question is the focus of the study, and it
impacts the selection of various elements of research, particularly data analysis and
finding results (Saunders et al., 2019). I used critical themes identified during the coding
process relevant to the research question and the conceptual framework for the study’s
interpretation of findings.
Reliability and Validity
Research design and procedures are checked for reliability and validity to achieve
acceptable quality work, particularly in qualitative and quantitative studies using key
research questions. Yin (2018) recognized construct, internal, and external validity and
reliability as standards to justify research design excellence. Although, construct and
internal validity are applied to a quantitative study to quantify and correlate two or more
variables (Yin, 2018). To verify the consistency and accuracy of this study, reliability,
validity, credibility, dependability, transferability, confirmability, and data saturation are
crucial to presenting quality research in this explorative study.
Reliability
The replication of study to prove the reliability of similar observations from the
study results to mitigate bias and erroneous information is crucial to research quality
(Yin, 2018). To prove the reliability of a study, a researcher must document data, create
acceptable research archives, follow research protocols, and uphold established principles
instituted by the research experts (Yin, 2018). Documenting this information enables
another researcher to replicate the study by applying the same information to test for the
validity and reliability of the study. A qualitative researcher achieves reliability by

79
presenting detailed information on the methods they used to realize research constancy
from other investigators (Rose & Johnson, 2020). To prove the reliability of this study, I
used a qualitative multiple case study with semistructured interviews to collect data by
following research protocols identified in (Appendix A) to establish data for the
replicability and consistency of this study. A researcher can improve reliability by
presenting similar questions to all the participants to demonstrate a study’s precision and
methodology (Rose & Johnson, 2020). I presented similar interviews questions to all
participants for consistency for further reliability tests to enhance research quality.
Dependability
Evaluating the quality of the research method through dependability refers to the
degree to which a researcher can repeat a study using comparable methods (Stenfors et
al., 2020). For a study to achieve dependability, a qualitative researcher must explain the
design, documents, coding, and analysis to ensure other scholars can recreate the study
(Constantinou et al., 2017; McGinley et al., 2021). Korstjens and Moser (2018) noted that
an audit trail is an approach to confirm dependability and confirmability. l explored the
study protocols describing the selected method, design, data gathering techniques,
population, and sample size to enable other scholars with accurate information to
replicate this study and obtain similar results or results that might be unique to the
different participants they interviewed for their studies.
To ascertain this study’s reliability, credibility, and dependability, I interviewed
three participants and collected data using a recorded device with a similar approach,
transcribed interview data, reviewed journal field notes and participant’s flyer, and

80
analyzed data with NVivo software. Motulsky (2021) pointed out that member checking
is another strategy to ensure the validity of the research. I presented the interpreted data
to participants for clarification on answers collected during the interview. The participants
confirmed with feedback for the accuracy of response. I triangulated data using journal
field notes, interviews, and participant’s flyer to achieve reliability and dependability.
Braun and Clarke (2021) identified data saturation as when no new information emerges
in the data. I concluded with the sufficient data collection that helped me reach data
saturation when no new information, codes and thematic analysis developed in the study.
The information embedded in this research with three participants’ interviews and other
data sources following my research protocol provided sufficient data for the replicability
of this study.
Validity
Academic research deals with rigorous procedures to ascertain the legitimacy of a
study. Validity is part of the benchmarks to determine research plans inquiry and is
categorized into a construct, internal, and external (Yin, 2018). Moon (2019) stated that
triangulation is an essential method to apply in research to ascertain the evidence used in
research to guarantee validity, reliability, and trustworthiness. Additionally, triangulation
is a method of collecting information from additional source to improve rigor and data
saturation (Moon, 2019). I confirmed validity through data triangulation using recorded
interviews, notes, member checking, and reviewing the organizations existing
information from their websites.

81
Credibility
Credibility entails the comprehensive explanation of the study procedures and the
range in which the study represents reality (Constantinou et al., 2017). Liao and
Hitchcock (2018) presented that credibility involves a systematic approach at every phase
of research and following principles to achieve measures to necessitate credibility through
examining statements, proposals, analysis, and writing findings. I obtained credibility by
presenting various details of the study’s component accuracy from collecting interview data
to accurately reporting the participant’s actual contributions.
Additional credibility techniques necessary in qualitative research are
triangulation, member checking, data saturation, and audit trail. Daniel (2019) stated that
a researcher could gain credibility by meticulously accounting for data analysis and
confirmation of sources of data retrieved from participants. I improved credibility
through member checking of data interpretation and by a review of participant transcripts
for accuracy, triangulation of interview transcripts with organizational documents, journal
field notes, and my interview protocol. Among the numerous types of triangulations,
observer, theoretical, method, and data source (Ellis, 2019) identified, I used
methodological triangulation, which includes collecting data with two or more sources
involving similar methodologies. These methodologies encompassed using interviews
and explanation of written data to produce complete and supported research output (Ellis,
2019). Daniel (2019) explained that member checking is vital to achieving credibility for
a study through presenting the collected data to participants for confirmation. Data
saturation means inferring credibility when no new information emerges signifying, I

82
used sufficient and applicable data on various phases of research to respond to the
research question (see Stenfors et al., 2020).
Transferability
Transferability signifies conveying the research findings to other circumstances or
setting with other people (Constantinou et al., 2017; Lemon & Hayes, 2020; Lincoln &
Guba, 1985). To illustrate transferability, a researcher must use purposive sampling to
choose participants to obtain rich data worthy of transfer to others (Forero et al., 2018;
Ospina et al., 2017). I improved research transferability of this study by conducting
ethical research by offering a detailed interpretation of the participants’ answers to
interview questions. I also used a purposeful sample of three participants with a deeper
knowledge of the phenomenon to demonstrate the transferability of this study by other
researchers or readers. Dalkin et al. (2021) stated that NVivo is an important computed
assisted program that supports transparency by categorically detailing and substantiating
information creating an audit trail of the research steps. Merriam and Grenier (2019)
identified that offering rich, thick description is a significant approach to ensure the
generalization or transferability in qualitative research by individual researchers. I
accurately followed the data collection process and analysis procedures using NVivo
software, using orderly interview protocol, and was able to achieve data saturation to
illustrate the validity and reliability of the research interpretation. I must explain the
procedures of the study comprehensively through the research question and setting to
allow other researchers to use this research as a reference in their studies. Even

83
describing the research process will not guarantee that different researchers from various
part of the country using the same method will achieve the same findings of the study.
Other researchers could then compare the similarities and differences in the findings from
this study to their study because they used the same method.
Confirmability
Confirmability involves portraying the respondent’s experiences through data and
thoughts rather than the researcher's beliefs (Constantinou et al., 2017; Korstjens &
Moser, 2018). Ellis (2019) posits that quality research provides the trail of data
compilation and interpretations. I must document an organized audit trail of the data
analysis to allow research auditors to confirm and depend on this study by presenting the
true interpretation of recorded interviews and other data used for this research. De Kleijn
and Van Leeuwen (2018) suggested that the audit process gives a researcher a complete
approach to leave a trail of selections and judgment established to allow another person to
confirm the study. I used method triangulation, member checking to validate the
information received from participants, probing questions for clarification during the
interview, and a follow-up member checking interview when necessary to achieve
confirmability. When presenting findings, avoiding bias is vital to confirmability to
demonstrate research rigor.
Carcary (2020) explained that an audit trail comprises data and analysis of the
collected information. Other researchers recognized that an audit trail involves various
classifications: (a) raw data, (b) analysis notes, (c) coding notes, (d) research procedures
and trustworthiness notes, and (e) individual reflexive notes (Carcary, 2020; Korstjens &

84
Moser, 2018; Lincoln & Guba, 1985). Developing a detailed audit trail through field
notes, themes, findings, and summaries enabled me to reach trustworthiness in this study.
Data Saturation
Achieving data saturation is paramount in qualitative research to exhaust relevant
information on the concept. Hennink and Kaiser (2019) noted that saturation is a
fundamental standard applied in a qualitative exploration to establish sufficient data to
create a solid and acceptable understanding of the research facts. Data saturation gives
research validity and is a part of the measures to evaluate qualitative research distinction
(Hennink & Kaiser., 2019). Member checking by participants is another tactic to reach
data saturation to ensure the confirmation and accuracy of the information collected.
Additionally, interviewing participants to collect data completed data saturation
when no new information was needed. Alam (2020) added that data saturation means no
new codes and findings resulting from data gathering and analysis. Saunders et al. (2019)
maintained that data saturation enables researchers to attain data capability and expand
the robustness of a qualitative case study. I reached data saturation in this research when
there was no new information forthcoming from the three participants. Member checking
was the primary method to ensure the participant understood the questions and that I
understood their answers.
Transition and Summary
In section 2, I presented the synopsis of the design of qualitative multiple case
studies to explore strategies private health insurance managers use to increase health
literacy on medical utilization to reduce healthcare costs. The proceeding explanations

85
involved the data collection instrument, techniques, organization, analysis, reliability, and
validity of the study. Additionally, Section 2 involved the aim of the study, the purpose
statement, the explanation, and experiences relating to the role of the researcher, the
participant's method of selection, the justification of research method and design,
population and sampling, plus ethical research protocol. Section 3 encompassed the
introduction, the presentation of the findings, application for professional practice, the
implication for social change, the recommendation for action and future research,
reflection, and conclusion.

86
Section 3: Application to Professional Practice and Implications for
Change
In this section, I presented the multiple-case study research findings, explained the
application of my study to professional practice, discussed the implication for social
change, the recommendations for actions, and the explanation of potential areas for
further research. Furthermore, I included my reflection on the research process and
experiences and finally the research study.
Introduction
This qualitative multiple case study aimed to explore private health insurance
managers strategies to increase patients' healthcare literacy on medical utilization to
reduce healthcare expenses. I used methodological triangulation involving,
semistructured interviews, my field journal notes, and the participant flyer encompassing
the health literacy program for the study. I presented eight semistructured interview
openended questions to three participants through Zoom videoconferencing. The
individual participants received an invitation letter and a consent form to participate in the
study before the interview. Each participant agreed by signing to participate and permit
the recording of the discussions. I replaced the participants’ identities with P1, P2, and P3
codes to ensure confidentiality.
The semistructured interviews lasted for less than 45 minutes for each participant.
I transcribed the recorded interviews, read through the data, and emailed my
interpretation for follow-up member-checking after a few days of conducting the
interviews. The participants responded with positive confirmation. Motulsky (2021)
identified that members of academic reviews deemed member checking relevant in

87
addressing threats to validity in research. I ensured each participant received my
interpretation of their answer for member checking. I imported the interview transcripts to
NVivo software to code, analyze, and create themes from the data collected from
participants. I examined data from the study using NVivo 12 to identify major emergent
themes. The four major themes that emerged from the data were (a) patient case
management engagement to achieve compliance, (b) continuous patient health education,
(c) health service utilization review, and (d) providers-patients collaboration.
Presentation of the Findings
The research question for the study was: What strategies do private health
insurance managers use to increase patients’ health literacy on medical utilization to
reduce healthcare expenses. I selected the HBM and Andersen HSU model as the
conceptual framework for my guide for this study. I conducted an exploratory study using
a qualitative multiple-case study to address my research question by gathering data from
three private health insurance agency managers. Using purposive sampling enabled me to
sample three participants with the knowledge and expertise important for the study. The
examination of interview data facilitated me in forming four core themes: (a) patient case
management engagement to achieve compliance, (b) continuous patient health education,
(c) health service utilization review, and (d) providers-patient collaboration.
Theme 1: Patient Case Management Engagement to Achieve Compliance
Participants expressed that patient interaction through case management is vital to
reaching each patient one-on-one to identify their health concerns and how to mitigate
further health problems. The intervention of health insurance case managers ensures that

88
a patient gets an explanation of all the health benefits and resources available to them and
various ways patients can save money for the insurance company to reduce health care
costs. P1 and P2 emphasized the importance of the patient’s case management team and
pointed out various strategies connected to patient case management engagement to
achieve compliance. Participants identified several strategies for case management:
Targeted communication and patient follow-up. P1 stated:
I think it's very important for any organization to have a case management
program because that one-on-one contact with the patient will give those
members the assurance that they have someone out there from their insurance,
that is able, or that they can just call and ask any medical questions.
P1 explained that his team interviews patient to understand the level of health literacy and
barriers to receiving health services to explain their specific disease condition, symptoms,
and how to manage the disease at home to mitigate future expenses. P1 expressed the
importance of one-on-one interaction with their health insurance member to understand
the holistic problem to better direct adequate health service utilization and reduce
healthcare costs. P1 stated:
The patient needs to be compliant, and if they are compliant. They fully
understand their illness and their treatments, their medication, it actually
prevented those members ending up in the hospital, which is, you know,
hospitalization is very expensive for those members, and for the insurance as
well, because every time you end up in the hospital, you have co-pays.

89
P2 explained, “ultimately, a patient is going to have a disease, and it's going to progress
unless they're super compliant, 100% compliant.” P1 and P2 emphasized the significance
of patient compliance in healthcare to achieve adequate medical utilization to reduce
healthcare costs. P3 expressed the benefit of targeted communication to address
individuals’ overall health concerns and barriers. P3 stated, “we have to serve not only
medically, but a whole person model, which is also their mental health.” P3 elaborated
that her team incorporated questions exceeding medical problems such as, are you in
danger or harm, do you experience domestic violence, depression, or suicide to better
educate members. P1 and P2 expressed the need for member follow-up for services and
its effectiveness for the continuation of progress in healthcare utilization to mitigate
frequent unnecessary ER visits and hospitalization. P1stated, “When my team receives
those referrals, what we do is we contact the patient, we make our research, read the
medical records from the hospital and find out exactly what happened.” P1 continued:
What's going on, what kind of testing do they have, and what type of follow-up they have
to do, now that they are out of the hospital? And we also checked on the clinic side,
where on the outpatient side, were prior to being admitted to the hospital, what kind of
follow-up the patient had? Were they compliant with their primary care doctors, follow
up, or with their medications?
Multiple scholars have confirmed the efficiency of health literacy programs in various
organizations in addressing healthcare utilization and the importance of reducing
healthcare costs.

90
P1 explained the impact of the implementation of Care for Me Program to assist and
support members with health education. P1 shared that there is a significant result for
members who participated in the health literacy program after 6 weeks of completing the
program. This finding corresponded with the existing and current literature validating the
impact of health literacy program interventions on mitigating disease
Findings Related to the Conceptual Framework and Literature
The conceptual frameworks for this study were HBM, dealing with behavioral
change, and HSU, which supports healthcare needs, predisposing factors, and access.
These two models were crucial for managers in understanding why individuals refuse to
obtain healthcare services and why some individuals do not have access to healthcare.
The frameworks were relevant to patient case management engagement to achieve
compliance in the intervention process to motivate behavioral change. This finding aligns
with the HBM and HSU models of health behavior and health service access.
Furthermore, managers serve as an intervention agent to motivate patients’ self-efficacy
that predicts cues to action with the understanding of disease susceptibility and severity of
illness while removing perceived barriers to treatment.
Additionally, patient-case manager engagement that promotes health behavior
compliance aligns with the justification to partake in health services utilization. The
various HBM constructs tied into this study finding on assessing an individual’s health
belief as a predictor of healthcare use. The result of this study also supports the current
research on healthcare managers’ engagement effort to achieve compliance,
corresponding with Reinhart et al. (2022) study on the importance of amplified

91
engagement during the COVID-19 pandemic using numerous modalities to achieve
patient compliance to reduce hospital- acquired conditions. As a result, the finding
identified that healthcare managers must commit to engagement with patients as a
strategy to increase health service compliance to mitigate health conditions to reduce
health expenses.
Theme 2: Continuous Patient Health Education
P1 mentioned that her team implemented Care for Me Program to educate patients
on their health conditions to address health education and wellness. Patients are at various
levels of education and health literacy. Participants were health insurance case managers
who helped educate members on their specific illness and home healthcare services and
explained the differences between urgent care and emergency department visits. P1 said:
We have this program called H. E. W, which is a health education and wellness program,
and what they do is they have certified diabetic counselors that do diabetic teaching or
diet modification, so it’s a 6-week program that the patient can either do telephonic or
they can also go to the clinic setting where they attend classes.
P1 commended the effect of the specific disease diabetic program on behavioral health
change in patients who participated. This finding agrees with Hu’s et al. (2022)
discoveries on the impact of patient-centered health education in encouraging and
affecting behavioral change for participants in the study.
P1 continued:
The purpose of the program is to make the patient understand the illness, like
diabetes and the treatments that are for that particular illness and make sure that

92
they also understand the medications that they're taking, including insulin, and
also the diet.
P2 explained that they have a continuous house call program through a nurse, social
worker, or case manager to support patients’ needs. P3 expressed that education involving
the whole person’s care model, which encompasses health, education, and wellness is an
important approach her team uses in achieving health literacy. P3 continued, “we ensure
that our members are aware of their health condition, if they are diabetic, they need to
have an endocrine appointment and optometry appointment and hemoglobin, an A1C test
every year through sending out flyers to educate patients.” P3 justified that they are
regulated by the National Committee for Quality Assurance (NCQA) to meet the various
benchmark. One of the benchmarks was to use fifth-grade level English to ensure that
patients understood the content of the information.
The overall goal for continuing education through case management is to educate
patients on the most cost-effective ways of caring for themselves to benefit both patients
and the insurance companies. P1 explained the impact of implementing of the Care for
me Program to assist and support members with health education. P1 reiterated that there
was significant progress for members who participated in the health literacy program
after 6-week of completing the program corresponded with Hu et al. (2022) literature
findings validating the impact of health literacy program interventions on mitigating
diseases and improving the quality of life. Martos-Cabrera et al. (2021) and other scholars
have confirmed the efficiency of rigorous health education interventions in various
studies collaborating with the P1, P2, and P3 findings.

93
Findings Related to the Conceptual Framework and Literature
According to literature on HBM, continuous health education produced positive
medical outcomes for women of child-bearing age battling cancer (Chalambari et al.,
2022). The findings from theme 2 corroborated with Chalambari’s et al. (2022) recent
literature findings on the impact of HBM constructs on disease intervention like breast
cancer before and after health literacy intervention. Hu et al. (2022) confirmed the
significance of the HBM in a nursing intervention program related to patients with
endstage renal disease improving medication intake and long-term management. The
impact of patient’s continuous health education was observed in the fight against the
COVID-19 pandemic. Although the process was challenging at first, the effect of regular
hygiene protocols and later vaccination drastically slowed the death rate, confirming
health education impact.
The finding from theme 2 paralleled with HSU in indicating the consideration
leading to health services use. Healthcare managers aid in understanding the enabling,
predisposing, and need capabilities of a patient. In the case of health insurance, the
predisposing concern is having access to health insurance and support to obtain health
services. P2 mentioned that patients might have access to health insurance but unable to
understand the benefits linked to service. Hajek et al. (2021) confirmed that predisposing,
enabling, and need factors were the determinants of HSU in the homeless population.
Theme 3: Health Service Utilization Review
Utilization review allows health care providers and patients to understand their
health service utilization rate and services economically necessary for patients. P1 and P2

94
identified that utilization review enables them to measure the impact of the health literacy
program and identify patients with extremely high utilization rates. Participants shared
that utilization review also measures readmission rate and emergency room utilization to
identify those patients in the group of high utilization to focus on helping them reduce
high utilization and costs. P2 mentioned that his team measured patient utilization rate
with the length of hospital stay, acuity of admission, comorbidity, and emergency visits
(LACE) score. Another measure is running of monthly numbers on health service
utilization and readmissions to prioritize care based on the score. P2 added that the higher
the LACE score, the more attention the team gives to the patient.
P1 highlighted the impact of the health literacy program before and after
participation to determine the effectiveness of the program. P1 stated that patients who
frequent the ER had reduced visits after completing the six weeks Care for Me Program
and did not visit the ER in three months. P3 expressed that the case managers in the
quality department would conduct an annual data review on the number of screenings to
determine an increase or decrease in participation. P3 shared:
We educate them on how to do the different utilization reviews kind of a thing.
We explain to them how each and every service that we offer from the health plan
is there to help benefit them in whatever way.”
P3 continued, “The other thing we do is online member evidence of coverage or evidence
of benefits.” Participants explained that a utilization review is necessary to access proper
care for a patient.

95
Findings Related to the Conceptual Framework and Literature
Conducting a health service utilization review is essential to comprehending
patients’ utilization rate. The finding tied into the second conceptual framework of this
study, the Andersen health service use. The factors of this framework, the enabling,
predisposing, and needs, were essential to understanding patients’ possibilities for
healthcare access and use. The participants mentioned that a patients utilization rate is
determined through monitoring the emergency department and hospitalization use.
Patients with abnormal healthcare use were given priority in mitigating factors
contributing to the problem. Participants shared that conducting a utilization review was a
vital strategy to increase health education with disease-specific literacy.
As the world faced the challenges of the COVID-19 pandemic, the disruption of
the necessary health service was evident in more than 100 countries (WHO, 2020). Saso
et al. (2020) and WHO. (2020) found that health service utilization disruption differed
according to country; developed countries encountered outpatient slowdown and
vaccination concerns during COVID-19. Saso and WHO identified that developing
countries suffered from the health service use gap, low supplies of workers, and medical
necessities. This literature showed the disparities in health service use among countries,
which also exist in individuals’ health beliefs. Further unforeseeable disruptions could
threaten the healthcare delivery system without adequate supply of healthcare workers
and equipment. Participants mentioned that service utilization review was a significant
strategy to support health utilization and reduce healthcare costs.

96
Theme 4: Providers-Patients Collaboration
The participants explicitly shared that multiple teams are involved in achieving
effective continuous health education for private insurance members to reduce costs. The
group includes, patients, physicians, case managers, nurse practitioners, social workers,
and others. P1 and P3 explained that working as a team has helped case managers
communicate with members to identify various barriers patients face in obtaining
healthcare screening and follow-up. Targeted communication and patient follow-up
services were the strategies participants used to accomplish provider-patient
collaboration. P3 added that a team of providers collaborated in providing different
services to ensure patients received quality care through follow-up and asking specific
questions related to preventative care. P3 mentioned:
We introduce the screening. A lot of it is pre-screenings because, you know,
preventative care is better than reactive care. So, when you have preventative
care, like screening for whole, and capture at a certain age, or screening for breast
cancer, asking women to get mammograms done at a certain age, and sending out
the flyers and getting the primary care physicians (PCP), case managers, and
everybody on board to educate them, hey? Have you had this done yet, because
this is like not a requirement, but a recommendation to make sure that you know
you don't get cancer? It helps to save costs, because if we can get care early on, it
doesn't cost us much later down the road.
Effective interactions between the healthcare professionals and the patients are
vital in achieving paramount health for the population. P1 suggested that the need for

97
electronic medical records to avoid the duplication of services is crucial in the
collaboration of health information providing authorized access to medical records. P1
cited an incident where a patient completed a laboratory service and the physician
unknowingly asked the patient to complete the same test; with P1’s intervention, the
patient obtained his medical record and avoided the costs associated with a new test. P2
stated that a team of interpreters for various languages, nurses, and nurse practitioner’s
coordinate with patients to educate and coordinate health service appointments. P2 added
that this team is available around the clock to address any medical concern and assist
patients in assessing their condition to decide to treat at home, go to the emergency
department, or urgent care.
Findings Related to the Conceptual Framework and Literature
The health belief model (HBM) and the Andersen health service utilization (HSU)
models were the conceptual framework for this study which identifies the relationships
between health behavioral change and individual’s actions that justifies and envisages
attitudes concerning health service use. The HBM, as a social psychological health
behavioral change standard, its relevance in the behavioral health research, particularly in
this study, enabled understanding related to health service use and belief.
ProvidersPatients HSU model in understanding an individual behavioral, predisposing,
enabling, and need factors. Participant 1 identified that holistic attention to behavioral
health is crucial to determining an individual’s health belief and perceived barriers to
health service use.

98
Understanding the HBM and HSU might facilitate health insurance managers’
knowledge in creating interventions to increase health service utilization through health
literacy. During the process of data examination, I identified themes and strategies private
health insurance managers use to increase patients' healthcare literacy on medical
utilization to reduce healthcare expenses. I found relevant emerging themes from the
study data which tie to HBM and HSU, (a) Patient case management engagement to
achieve compliance, (b) Continuous patient health education (c) Health service utilization
review, which ties into the Andersen health service utilization model and (d)
providerpatient collaboration. The Andersen health service utilization is significant in
identifying patient’s or member’s needs and barriers to accessing healthcare services.
Table 2
Summary of Themes to Increase Utilization to Reduce Healthcare Costs
Themes
P1
P2
P3
Patient case
management
100%
100%
100%
Continuous patient
health
education
100%
100%
100%
Health service
utilization
review
100%
100%
100%
Provider-
patient
collaboration
100%
100%
100%

99
Applications to Professional Practice
After exploring the strategies private health insurance organizations use to
increase patient health literacy on medical utilization, four themes emerged. The findings
from this study revealed that patient case management engagement to achieve
compliance, continuous patient health education, health service utilization review, and
providers-patient collaboration were significant in increasing patient health literacy. The
participants mentioned that engaging in such strategies as targeted communication,
patient follow-up services, team collaboration, and identifying barriers were important in
mitigating healthcare costs. Although the study was specific to Las Vegas, Nevada, the
findings might be relevant to other areas. The results will enhance the professional
practice of business because private, and public health insurance companies bear the
financial responsibilities of healthcare members. Understanding strategies to increase
health literacy on medical utilization to reduce healthcare costs will benefit health
insurance practitioners in the area of preventing disease progression through early
dictation to increase profitability.
Implications for Social Change
The implication for social change involves awareness of adequate health literacy
strategies to increase medical utilization to reduce healthcare costs. The result from this
study is crucial in understanding how to educate patients through various collaborative
programs to increase annual screenings to identify diseases early, manage specific
conditions, and reduce healthcare expenses. The increasing healthcare costs in the United

100
States have impacted a significant portion of the population financially, especially
persons with comorbidity. Seeking early health intervention using the findings from this
study may mitigate late diagnosis leading to death. The result of this study might
potentially promote social change in health literacy education for organizations and
improve individuals’ knowledge on managing and initiating health screening, thereby
reducing costs by avoiding expensive fees related to chronic diseases. This finding holds
the potential for social change to enhance communities’ health literacy awareness and
enrich institutional database for students and researchers. This finding might also trigger
a social change through government policymakers in understanding the significance of
health literacy to increase medical utilization to reduce healthcare costs.
Recommendations for Action
Several recommendations developed from my findings and academic literature.
These recommendations are imperative for health insurance managers and other
healthcare professionals responsible for managing patients’ health and increasing medical
utilization to reduce healthcare costs. The findings of this study involve four themes (a)
patient case management engagement to achieve compliance, (b) continuous patient
health education, (c) health service utilization review, and (d) providers-patient
collaboration. The following are the recommendations for health insurance managers and
healthcare professionals to consider: First, managers must understand the level of health
literacy for individuals prior to program implementation. Second, accessing patients’
understanding of HBM entails health behavior, and HSU predicts one’s need,
predisposing influences, and enabling elements to receive healthcare services. Third, the

101
study findings were essential to demonstrate the effect of health literacy education on
improving of health. Therefore, I recommend that managers and other professional
medical staff continue to enhance their education on health literacy to better support
patients with low health literacy.
After the publication of this study on ProQuest, I can disseminate the findings to
health insurance managers in Nevada seeking health literacy strategies to increase
medical utilization to reduce healthcare costs. The result of this study might be useful in
health education intervention conferences for healthcare professionals and institutions.
Publication in the health sciences and business management journals will also be
necessary to disseminate the study findings.
Recommendations for Further Research
The purpose of this qualitative, multiple case study is to explore the strategies
private health insurance managers use to increase patients' health literacy on medical
utilization to reduce healthcare expenses. Emulating the strategies emergent from this
study might be essential in creating more awareness for adequate utilization of medical
resources, which would benefit the population and lessen the rising healthcare costs for
individuals and the country. The study results are informative but further research is vital
to improve health literacy knowledge and identify how to incorporate the emerging health
technologies devices to alert individuals to conduct health screenings. The limitations and
recommendations for this study are part of my personal experiences completing this
research.

102
There are two limitations to this study. The first limitation is the challenge of
recruiting participants and collecting answers not related to the question. To address this
limitation, I used probing questions to obtain more detail in receiving responses directed
to the questions. The second limitation was the sample size of three participants may not
be sufficient to identify strategies other organizations use. I received enough information
from the three interviews to reach data saturation and the triangulation of other sources
using field notes and participant’s public information. The recommendation for further
research is for other researchers to repeat this study using the quantitative or mixed
method to include a larger sample size from a national health database to understand
different strategies. A second recommendation is to extend this research to other
geographical areas outside Nevada to yield similar or dissimilar results adding to more
approaches to increase health literacy on medical utilization to reduce healthcare costs.
The final recommendation is to encourage more research on why many health
literate persons (i.e., nurses and doctors who would be considered highly health literate)
refused to get their Covid shots as a preventative measure. The healthcare providers
should know better than persons who have taken the advice but may just be considered
average in their health literacy knowledge. This situation is puzzling and contradictory
because health literacy is vital in improving healthcare outcomes in the United States and
other countries worldwide. There is a lot more that we need to learn that is still a mystery
to people who ask these questions.

103
Reflections
My experience within the Doctor of Business Administration (DBA) program
process was a mixture of challenges, advancement of knowledge, and academic
progression. Through this process of exploring strategies private health insurance
companies use to increase patient health literacy on medical utilization to reduce
healthcare costs, I learned that bias is inevitable, Still, I stayed neutral, objective, and
focused on the interview protocol for data collection and analysis of the factual
information as collected. The absence of a traditional face-to-face interview that I
anticipated brought the challenges of not identifying the participants’ body language
concerning the questions. In this study, there is the absence of personal interaction from
in data gathering process, although it was convenient and low cost. I triangulated the
interview data, field notes, and member-checking to avoid researcher bias.
The potential effect of the research on participants is the reward of contributing to
this study. P1 and P2 stated that they were glad to contribute to this study. The
participants contributed valuable insight to identifying effective strategies to increase
patient health literacy on medical utilization to reduce healthcare costs. The most
significant participants collective contribution to this study was the importance of
continuous health literacy education and team case management. The contribution might
aid healthcare professionals in providing adequate health education on medical utilization
to prevent the advancement of diseases and to achieve cost reduction. After completing
this research study, the experience of a DBA journey has changed my perspective on the
requirements to obtain a doctoral degree in time and commitment. The entire

104
understanding of my doctoral study journey has advanced my research knowledge in
conducting semi-structured interview.
Conclusion
Several studies identified low health literacy as one of the significant reasons for
insufficient access to health-related services. Some individuals with inadequate health
literacy are prone to not engage in health-related information due to low self-efficacy in
understanding the information to make health decisions. The World Health Organization
has recognized a global need to increase the rate of patients’ health literacy. Studies have
found that a patient’s psychological readiness, autonomous health commitment, and
provider's encouragement determine the level of health literacy (Graffigna et al., 2016).
Low healthcare literacy does not explain all of the reasons why some medical
professionals and other persons have refused to seek treatments to prevent the spread of
infectious diseases like COVID-19.
Some private health insurance managers lack strategies to increase patients'
healthcare literacy on medical utilization to reduce healthcare expenses. The purpose of
this qualitative, multiple case study was to explore the strategies private health insurance
managers use to increase patients' healthcare literacy on medical utilization to reduce
healthcare expenses. The critical theme in this study is that health literacy involves
multiple teams and case managers to continuously educate the population on healthcare
concerns to achieve preventive care and longevity, leading to a better quality of life and
increased productivity and profitability for healthcare organizations and individuals. The
results from this study indicated the importance of implementing effective strategies to

105
increase healthcare literacy. The findings could also aid healthcare managers and other
business owners in understanding the need to implement health literacy programs within
organizations. The key recommendation for private health insurance managers is to work
collaboratively to meet patient health literacy needs to reduce costs. By working together,
success can be achieved with those persons who are open to suggestions and
encouragement from their healthcare professionals.

106
References
Abadie, R., Fisher, C., & Dombrowski, K. (2021). “He's under oath”: Privacy and
confidentiality views among people who inject drugs enrolled in a study of social
networks and human immunodeficiency virus/hepatitis C virus risk. Journal of
Empirical Research on Human Research Ethics, 16(3), 304–311.
https://doi.org/10.1177/15562646211004411
Abdalla, M. M., Oliveira, L. G. L., Azevedo, C. E. F., & Gonzalez, R. K. (2018). Quality
in qualitative organizational research: Types of triangulations as a methodological
alternative. Administração: Ensino E Pesquisa, 19(1), 66–98.
https://doi.org/10.13058/raep.2018.v19n1.578
Abdel-Latif, M. M. M. (2020). The enigma of health literacy and COVID-19 pandemic.
Public Health, 185, 95–96. https://doi.org/10.1016/j.puhe.2020.06.030
Agency for Healthcare Research and Quality. (2020). Health literacy universal
precautions toolkits.
https://www.ahrq.gov/healthliteracy/improve/precautions/index.hmtl
Alam, M. K. (2020). A systematic qualitative case study: Questions, data collection,
NVivo analysis and saturation. Qualitative Research in Organizations, and
Management, 16(1), 1–31. https://doi.org/10.1108/QROM-09-2019-1825
Alexander, B. N., & Smith, A. D. (2019). Organizational access in qualitative research.
Qualitative Research in Organizations and Management: An
International Journal, 14(2), 172–193. https://doi.org/10.1108/QROM-10-2017-
1574
107
Alsulaiman, S. A., & Rentner, T. L. (2018). The health belief model and preventive
measures: A study of the ministry of a health campaign on coronavirus in Saudi
Arabia. Journal of International Crisis and Risk Communication Research, 1(1),
27–56. https://doi.org/10.30658/jicrcr.1.1.3
Andersen, R. M. (2008). National health surveys and the behavioral model of health
services use. Medical Care, 46(7), 647–653.
http://www.jstor.org/stable/40221718
Asmundson, G. J., & Taylor, S. (2020). How health anxiety influences responses to viral
outbreaks like COVID-19: What all decision-makers, health authorities, and
health care professionals need to know. Journal of Anxiety Disorders, 71,1–3.
https://doi.org/10.1016/j.anxdis.2020.102211.
Ataro, G. (2020). Methods, methodological challenges, and lesson learned from
phenomenological study about OSCE experience: Overview of paradigm-driven
qualitative approach in medical education. Annals of Medicine and Surgery, 49,
19–23. https://doi.org/10.1016/j.amsu.2019.11.013
Barello, S., Palamenghi, L., & Graffigna, G. (2020). The mediating role of the patient
health engagement model on the relationship between patient perceived autonomy
supportive healthcare climate and health literacy skills. International Journal of
Environmental Research and Public Health, 17(5), Article e1741.
https://doi.org/10.3390/ijerph17051741
Bartsch, S. M., Ferguson, M. C., McKinnell, J. A., O’Shea, K. J., Wedlock, P. T.,
Siegmund, S. S., & Lee, B. Y. (2020). The potential health care costs and resource
108
use associated with COVID-19 In the United States: A simulation estimate of the
direct medical costs and health care resource use associated with COVID-19
infections in the United States. Health Affairs, 39(6), 927–935.
https://doi.org/10.1377/hlthaff.2020.00426
Basias, N., & Pollalis, Y. (2018). Quantitative and qualitative research in business &
technology: Justifying a suitable research methodology. Review of Integrative
Business and Economics Research, 7, 91–105.
https://sibresearch.org/uploads/3/4/0/9/34097180/riber_7-s1_sp_h17-083_91-
105.pdf
Bergen, N., & Labonté, R. (2020). “Everything is perfect, and we have no problems:”
detecting and limiting social desirability bias in qualitative research. Qualitative
Health Research, 30(5), 783–792. https://doi.org/10.1177/1049732319889354
Berkowitz, S. A., Seligman, H. K., Meigs, J. B., & Basu, S. (2018). Food insecurity,
healthcare utilization, and high cost: A longitudinal cohort study. The American
Journal of Managed Care, (24)9, 399–404.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6426124/
Berndt, A. E. (2020). Sampling methods. Journal of Human Lactation, 36(2), 224–226.
https://doi.org/10.1177/0890334420906850
Bhardwaj, P. (2019). Types of sampling in research. Journal of the Practice of
Cardiovascular Sciences, 5(3), 157–163.
https://www.jpcs.org/text.asp?2019/5/3/157/273754
Bingley, A. (2020). An introduction to narrative research methods in health and social
care. In C. Walshe & S. G. Brearley (Eds.), Handbook of Theory and Methods in

109
Applied Health Research. (pp. 107–127). Edward Elgar Publishing.
https://doi.org/10.4337/9781785363214.00013
Birt, L., Scott, S., Cavers, D., Campbell, C., & Walter, F. (2016). Member checking: A
coding tool to enhance trustworthiness or merely a nod to validation? Qualitative
Health Research. 26(13), 1802–1811. https://doi.org/10.1177/1049732316654870
Blendon, R. J., Benson, J. M., & McMurtry, C. L. (2019). The upcoming US healthcare
cost debate-the public's views. The New England Journal of Medicine, 380(26),
2487–2492. https://doi.org/10.1056.NEJMp1905710
Boddy, C. R. (2016). Sample size for qualitative research. Qualitative Market Research:
An International Journal, 19(4), 426–432. https://doi.org/10.1108/QMR-06-2016-
0053
Brach, C., & Harris, L. M. (2021). Healthy People 2030 health literacy definition tells
organizations: Make information and services easy to find, understand, and use.
Journal General Internal Medicine. 36(4), 1084–1085.
https://doi.org/10.1007/s11606-020-06384-y
Braun, V., & Clarke, V. (2021). To saturate or not to saturate? Questioning data
saturation as a useful concept for thematic analysis and sample-size rationales.
Qualitative Research in Sport, Exercise, and Health, 13(2), 201–216.
https://doi.org/10.1080/2159676X.2019.1704846
Burkholder, G. J., Cox, K. A., Crawford, L. M., & Hitchcock, J. H. (Eds.).
(2019). Research design and methods: An applied guide for the scholar-
practitioner. Sage Publications.

110
Bush, M. (2018). Addressing the root cause: Rising health care costs and social
determinants of health. North Carolina Medical Journal, 79(1), 26–29.
https://doi.org/10.18043/ncm.79.1.26
Çakar, K., & Aykol, Ş. (2021). Case study as a research method in hospitality and tourism
research: A systematic literature review (1974-2020). Cornell Hospitality
Quarterly, 62(1), 21–31. https://doi.org/10.1177/1938965520971281
Candela, A. G. (2019). Exploring the function of member checking. The Qualitative
Report, 24(3), 619–628. https://doi.org/10.46743/2160-3715/2019.3726
Carcary, M. (2020). The research audit trail: Methodological guidance for application in
practice. Electronic Journal of Business Research Methods, 18(2), 166–177.
https://doi.org/10.34190/jbrm.18.2.008
Centers for Medicare and Medicaid Services. (2017). Projections of national health
expenditures: Methodology and model specification. https://www
.cms.gov/Research-Statistics-Data-and-Systems/Statistics-Trends-and-Reports
/NationalHealthExpendData/downloads/projectionsmethodology.pdf.
Centers for Medicare and Medicaid Services. (2020). National health expenditures 2019
highlights. https://www.cms.gov/Research-Statistics-Data-and-Systems/Statistics-
Trends-and-
Reports/NationalHealthExpendData/NationalHealthAccountsHistorical
Chalambari, S., Amin Shokravi, F., & Zarei, F. (2022). Breast cancer prevention
behaviors in women with low levels of health literacy of reproductive age:

111
Application of health belief model. Journal of Health Literacy, 7(2), 68–59.
https://doi.org/10.22038/jhl.2022.61960.1247
Cheng, Y., Goodin, A. J., Pahor, M., Manini, T., & Brown, J. D. (2020). Healthcare
utilization and physical functioning in older adults in the United States. Journal of
the American Geriatrics Society, 68(2), 266–271.
https://doi.org/10.1111/jgs.16260
Chini, L. T., Caliari, T. M., Alves De Oliveira, L. F., Passos Nogueira, T. C., Nascimento,
M. C., & da Silva, S. A. (2019). Integration of methodological references for the
preparation of case studies. Journal of Nursing UFPE /Revista de Enfermagem
UFPE, 13(1), 249–253.
https://doi-org/10.5205/1981-8963v13i01a238405p249-253-2019
Chisolm, D. J., Keedy, H. E., Hart, L. C., Chavez, L. J., Dolce, M., Morack, J., Grannis,
C., & Kelleher, K. (2021). Exploring health literacy, transition readiness, and
healthcare utilization in Medicaid chronically ill youth. Journal of Adolescent
Health, 69(4), 622–628. https://doi.org/10.1016/j.jadohealth.2021.03.023
Cilliers, P. (2002). Complexity and postmodernism: Understanding complex systems.
Routledge.
Clark, C. M., Shaver, A. L., Aurelio, L. A., Feuerstein, S., Wahler, R. G., Daly, C. J., &
Jacobs, D. M. (2020). Potentially inappropriate medications are associated with
increased healthcare utilization and costs. Journal of the American Geriatrics
Society, 68(11), 2542–2550. https://doi.org/10.1111/jgs.16743
Constantinou, C. S., Georgiou, M., & Perdikogianni, M. (2017). A comparative method
for themes saturation in qualitative interviews. Qualitative Research,
112
17(5), 571–588. https://doi.org/10.1177/1468794116686650
Creswell, J. W., & Hirose, M. (2019). Mixed methods and survey research in family
medicine and community health. Family Medicine and Community Health, 7(2),
1–6. https://doi.org/10.1136/fmch-2018-000086
Creswell, J. W., & Poth, C. N. (2017). Qualitative inquiry and research design: Choosing
among five approaches. Sage Publications.
Crossley, S. A., Balyan, R., Liu, J., Karter, A. J., McNamara, D., & Schillinger, D. (2020).
Predicting the readability of physicians’ secure messages to improve health
communication using novel linguistic features: Findings from the ECLIPPSE
study. Journal of Communication in Healthcare, 13(4), 344–356.
https://doi.org/10.1080/17538068.2020.1822726
Dalkin, S., Forster, N., Hodgson, P., Lhussier, M., & Carr, S. M. (2021). Using computer
assisted qualitative data analysis software (CAQDAS; NVivo) to assist in the
complex process of realist theory generation, refinement, and testing.
International Journal of Social Research Methodology, 24(1), 123–134.
http://doi.org/10.1080/13645579.2020.1803528
Dang, Y., Zou, G., Peng, B., & Ling, L. (2018). Health service seeking behavior among
migrant workers in small and medium-sized enterprises in Guangdong, China:
Does family migration matter? BioMed Research International, Article 3620436,
1–10. https://doi.org/10.1155/2018/3620436
Daniel, B. K. (2019). Using the TACT framework to learn the principles of rigor in
qualitative research. Electronic Journal of Business Research Methods, 17(3),
118–129. https://doi.org/10.34190/jbrm.17.3.002

113
Dankar, F. K., Gergely, M., & Dankar, S. K. (2019). Informed consent in biomedical
research. Computational and Structural Biotechnology Journal, (17), 463–474.
https://doi.org/10.1016/j.csbj.2019.03.010
DeJonckheere, M., & Vaughn, L. M. (2019). Semistructured interviewing in primary care
research: a balance of relationship and rigor. Family Medicine and Community
Health, 7(2), Article e000057. https://doi.org/10.1136/fmch-2018-000057
De Kleijn, R., & Van Leeuwen, A. (2018). Reflections and review on the audit procedure:
Guidelines for more transparency. International Journal of Qualitative
Methods, 17(1), 1–8. https://doi.org/10.1177/1609406918763214
Denzin, N. K. (1978). The research act: A theoretical introduction to sociological
methods (2nd ed.). McGraw Hill.
De Wit, L., Fenenga, C., Giammarchi, C., Di Furia, L., Hutter, I., de Winter, A., &
Meijering, L. (2018). Community-based initiatives improving critical health
literacy: A systematic review and meta-synthesis of qualitative evidence. BMC
Public Health, 18(1), 1–11. https://doi.org/10.1186/s12889-017-4570-7
El-Elimat, T., AbuAlSamen, M. M., Almomani, B. A., Al-Sawalha, N. A., & Alali, F. Q.
(2021). Acceptance and attitudes toward COVID-19 vaccines: A cross-sectional
study from Jordan. Plos One, 16(4), Article e0250555.
https://doi.org/10.1371/journal.pone.0250555
Elfil, M., & Negida, A. (2017). Sampling methods in clinical research; an educational
review. Archives of Academic Emergency Medicine, 5(1), e52
https://doi.org/10.22037/aaem.v5i1.177
114
Elgzar, W. T., Al-Qahtani, A. M., Elfeki, N. K., & Ibrahim, H. A. (2020). COVID-19
outbreak: Effect of an educational intervention based on health belief model on
nursing students' awareness and health beliefs at Najran University, Kingdom of
Saudi Arabia. African Journal of Reproductive Health, 24(2), 78–86.
https://doi.org/10.29063/ajrh2020/v24i2s.12
Ellis, P. (2019). The language of research (part 20): Understanding the quality of a
qualitative paper (2). Wounds UK, 15(1), 110–111.
https://www.woundsuk.com/journals/issue/570/article-details/language-research-
part-20understanding-quality-qualitative-paper-2
Etikan, I., Alkassim, R., & Abubakar, S. (2016). Comparison of snowball sampling and
sequential sampling technique. Biometrics and Biostatistics International
Journal, 1(3), 6–7. https://doi.org/10.15406/bbij.2016.03.00055
Fernandez, L. H. (2020). The right to withdraw from controlled human infection studies:
Justifications and avoidance. Bioethics, 34(8), 833–848.
https://doi.org/10.1111/bioe.12704
Ferreira, D. M. C., & Saurin, T. A. (2019). A complexity theory perspective of Kaizen: A
study in healthcare. Production Planning & Control, 30(16), 1337–1353.
https://doi.org/10.1080/09537287.2019.1615649
Fisher, J. A., McManus, L., Wood, M. M., Cottingham, M. D., Kalbaugh, J. M.,
Monahan, T., & Walker, R. L. (2018). Healthy volunteers’ perceptions of the
benefits of their participation in phase I clinical trials. Journal of Empirical
Research on Human Research Ethics, 13(5), 494–510.
https://doi.org/10.1177/1556264618804062

115
Fleary, S. A., & Ettienne, R. (2019). Social disparities in health literacy in the United
States. Health Literacy Research Practice, 3(1), e47–e52.
https://doi.org/10.3928/24748307-20190131-01
Fleary, S. A., & Joseph, P. (2020). Adolescents’ health literacy and decision-making: A
qualitative study. American Journal of Health Behavior, 44(4), 392–408.
https://doi.org/10.5993/AJHB.44.4.3
Forero, R., Nahidi, S., De Costa, J., Mohsin, M., Fitzgerald, G., Gibson, N., McCarthy,
S., & Aboagye-Sarfo, P. (2018). Application of four-dimension criteria to assess rigor
of qualitative research in emergency medicine. BMC Health Services
Research, 18(1), 1–11. https://doi.org/10.1186/s12913-018-2915-2
Frey, B. (Ed.). (2018). The Sage encyclopedia of educational research, measurement, and
evaluation, 1(4). Sage Publications. https://doi.org/10.4135/9781506326139 Fusch, P.,
Fusch, G. E., & Ness, L. R. (2018). Denzin’s paradigm shift: Revisiting triangulation
in qualitative research. Journal of Social Change, 10(1), 19–32.
https://doi.org/10.5590/JOSC.2018.10.1.02
Garg, S. (2020). The “economic health” of US healthcare and role of
middlemen. Diabetes Technology & Therapeutics, 22(2), 136–141.
https://doi.org/10.1089/dia.2019.0395
Gawron, A. J., Staub, J., & Bielefeldt, K. (2021). Impact of health insurance, poverty, and
comorbidities on colorectal cancer screening: Insights from the Medical
Expenditure Panel Survey. Digestive Diseases Sciences, 66(1), 70–77.
https://doi.org/10.1007/s10620-020-06541-7

116
Geddis-Regan, A. R., Exley, C., & Taylor, G. D. (2021). Navigating the dual role of
clinician-researcher in qualitative dental research. Journal of Dental Research
Clinical & Translational Research. 7(2), 215–217.
https://doi.org/10.1177/2380084421998613
Gellman, M. D., & Turner, J. R. (Eds.). (2013). Encyclopedia of behavioral medicine (pp.
1303–1304). Springer. https://doi.org/10.1007/978-1-4419-1005-9_885
Gephart, R. (2018). Qualitative research as interpretive social science. In the sage
handbook of qualitative business and management research methods, 33–53.
Sage Publications. https://doi.org/10.4135/9781526430212
Gossett, K., Padgett, J., Pierce, S., & Scott, J. (2019). Complex adaptive system theory
and the Tau conceptual framework for understanding healthcare and human
services in the United States. Journal of Academic Perspectives, 2019 (2),
1–28. https://www.journalofacademicperspectives.com/back-issues/volume-
2019/volume-2019-no-2/
Goto, E., Ishikawa, H., Okuhara, T., & Kiuchi, T. (2019). Relationship of health literacy
with utilization of health-care services in a general Japanese population.
Preventive Medicine Reports, 14, Article 100811.
https://doi.org/10.1016/j.pmedr.2019.01.015 Graffigna, G., Barello, S., Bonanomi, A., &
Menichetti, J. (2016). The motivating function of a healthcare professional in eHealth and
mHealth interventions for type 2 diabetes patients and the mediating role of patient
engagement. Journal of
Diabetes Research, (2016), Article 2974521.

117
https://doi.org/10.1155/2016/2974521
Green, E. C., Murphy, E. M., & Gryboski, K. (2020). The health belief model. The Wiley
Encyclopedia of Health Psychology, 211–214.
https://doi.org/10.1002/9781119057840.ch68
Gustafsson, J. (2017). Single case studies vs multiple case studies: A comparative study.
Academy of Business, Engineering and Science.
http://urn.kb.se/resolve?urn=urn:nbn:se:hh:diva-33017
Hajek, A., Bertram, F., Heinrich, F., van Ruth, V., Ondruschka, B., Kretzler, B., Schuler,
C., Puschel, K., & Konig, H. (2021). Determinants of health care use among
homeless individuals: Evidence from the Hamburg survey of homeless
individuals. BMC Health Service Research (21)1, 1–7.
https://doi.org/10.1186/s12913-021-06314-6
Halkias, D., & Neubert, M. (2020). Extension of theory in leadership and management
studies using the multiple-case study design. International Leadership Journal,
12(2), 48–73. https://doi.org/10.2139/ssrn.3586256
Hammersley, M., & Atkinson, P. (2019). Ethnography: Principles in practice, (2nd ed.).
Routledge.
Hargreaves, M. K., Mouton, C. P., Liu, J., Zhou, Y. E., & Blot, W. J. (2019). Adverse
childhood experiences and health care utilization in a low-income population. Journal of
Healthcare for the Poor and Underserved, 30(2), 749–767.
https://doi.org/10.1353/hpu.2019.0054

118
Hashemi-Shahri, S. M., Khammarnia, M., Ansari-Moghaddam, A., Setoodehzadeh, F.,
Okati-Aliabad, H., & Peyvand, M. (2020). Sources of news as a necessity for
improving community health literacy about COVID-19. Medical Journal of the
Islamic Republic of Iran, 34(1), 453–455. https://doi.org/10.47176/mjiri.34.63
Haslam, A., Crain, T., Gill, J., Herrera-Perez, D., & Prasad, V. (2019). Where does the
blame for high health care costs go? An empirical analysis of newspaper and
journal articles criticizing health care costs. The American Journal of Medicine.
132(6), 718–721. https://doi.org/10.1016/j.amjmed.2018.12.019
Hayden, J. (2017). Introduction to health behavior theory (3rd ed.). Jones & Bartlett
Learning.
Healthy People 2030, U.S. Department of Health and Human Services, Office of Disease
Prevention and Health Promotion (n.d.). Retrieved October 22, 2021, from
https://health.gov/healthypeople/objectives-and-data/social-determinants-health
Heath, J., Williamson, H., Williams, L., & Harcourt, D. (2018). “It's just more personal:”
Using multiple methods of qualitative data collection to facilitate participation in
research focusing on sensitive subjects. Applied Nursing Research, (43), 30–35.
https://doi.org/10.1016/j.apnr.2018.06.015
Hennink, M., & Kaiser, B. (2019). Saturation in qualitative research. In P. Atkinson, S.
Delamont, A. Cernat, J. W. Sakshaug, & R. A. Williams, (Eds.), Sage Research
Methods Foundations. https://doi.org/10.4135/9781526421036822322
Hickey, K. T., Masterson Creber, R. M., Reading, M., Sciacca, R. R., Riga, T. C., Frulla,
A. P., & Casida, J. M. (2018). Low health literacy: Implications for managing
cardiac patients in practice. The Nurse Practitioner, 43(8), 49–55.

119
https://doi.org/10.1097/01.NPR.0000541468.54290.49
Hochbaum, G., Rosenstock, I., & Kegels, S. (1952). Health belief model. The United
States Public Health Service. https://www.academia.edu
Holtrop, J. S., Rabin, B. A., & Glasgow, R. E. (2018). Qualitative approaches to use of
the RE-AIM framework: Rationale and methods. BMC health Services
Research, 18(1), 1–10. https://doi.org/10.1186/s12913-018-2938-8
Hoorani, B. H., Nair, L. B., & Gibbert, M. (2019). Designing for impact: The effect of
rigor and case study design on citations of qualitative case studies in management.
Scientometrics, 121(1), 285–306. https://doi.org/10.1007/s11192-019-03178-w
Hu, S., Xiong, R., Hu, Q., & Li, Q. (2022). Effects of nursing intervention based on
health belief model on self-perceived burden, drug compliance, and quality of
life of renal transplant recipients. Contrast Media & Molecular Imaging.
https://doi.org/10.1155/2022/3001780
Institute of Medicine. (2004). Health literacy: A prescription to end confusion. The
National Academies Press. https://doi.org/10.17226/10883
Iyamu, T. (2018). Collecting qualitative data for information systems studies: The reality
in practice. Education and Information Technologies, 23(5), 2249–2264.
https://doi.org/10.1007/s10639-018-9718-2
Janz, N. K., & Becker, M. H. (1984). The health belief model: A decade later. Health
Education & Behavior, 11(1), 1–47.
https://doi.org/10.1177/1090198 18401100101
120
Johnson, J. L., Adkins, D., & Chauvin, S. (2020). A review of the quality indicators of
rigor in qualitative research. American Journal of Pharmaceutical Education,
84(1), Article 7120. https://doi.org/10.5688/ajpe7120
Jones, J., & Smith, J. (2017). Ethnography: Challenges and opportunities. Evidence
Based Nursing, 20(4), 98–100. https://doi.org/10.1136/eb-2017-102786
Kallemeyn, L. M., Hall, J. N., & Gates, E. (2020). Exploring the relevance of complexity
theory for mixed methods research. Journal of Mixed Methods Research, 14(3),
288–304. https://doi.org/10.1177/1558689819872423
Karl, J. I., & McDaniel, J. C. (2018). Health literacy deficits found among educated,
insured university employees. Workplace Health & Safety, 66(9), 419–427.
https://doi.org/10.1177/2165079918758773
Kickbusch, I., Wait, S., Maag, D., & Banks, I. (2006). Navigating health: The role of
health literacy. Alliance for Health and the Future, International Longevity
Centre. https://ilcuk.org.uk/files/pdf_pdf_3.pdf
Kiger, M. E., & Varpio, L. (2020). Thematic analysis of qualitative data: Association for
medical education in Europe guide No. 131. Medical Teacher, 42(8), 846–854.
https://doi.org/10.1080/0142159X.2020.1755030
Killian, L., & Coletti, M. (2017). The role of universal health literacy precautions in
minimizing “Medspeak” and promoting shared decision making. American
Medical Association Journal of Ethics, 19(3), 296–303.
https://doi.org/10.1001/journalofethics.2017.19.3.pfor1-1703
121
Kim, H., Sefcik, J. S., & Bradway, C. (2017). Characteristics of qualitative descriptive
studies: A systematic review. Research in Nursing & Health, 40(1), 23–42.
https://doi.org/0.1002/nur.21768
Kirson, N. Y., Ou, S., & Gorry, J. (2020). How to think about value assessment of
medical services in the United States. Value in Health, 23(1), 299.
https://doi.org/10.1016/j.jval.2020.04.1089
Korstjens, I., & Moser, A. (2018). Series: Practical guidance to qualitative research. Part
4: Trustworthiness and publishing. The European Journal of General
Practice, 24(1), 120–124. https://doi.org/10.1080/13814788.2017.1375092
Košir, U., & Sørensen, K. (2020). COVID-19: the key to flattening the curve is health
literacy. Perspectives in Public Health, 142(5), 259–260.
https://doi.org/10.1177/1757913920936717
Krekeler, B. N., Vitale, K., Yee, J., Powell, R., & Rogus-Pulia, N. (2020). Adherence to
dysphagia treatment recommendations: A conceptual model. Journal of Speech,
Language & Hearing Research, 63(6), 1641–1657. https://doi-
.org/10.1044/2020_JSLHR-19-00270
Kross, J., & Giust, A. (2019). Elements of research questions in relation to qualitative
inquiry. The Qualitative Report, 24(1), 24–30.
https://www.nova.edu/ssss/OR/index.html
Kurnia, A. D., Masruroh, N. L., Melizza, N., & Rofi’i, A. Y. (2021). Factors associated
with preventive behaviors of COVID-19 among Indonesian nursing students: Application
of health belief model. Russian Open Medical Journal, 10(2), 1–6.
122
https://doi.org/10.15275/rusomj.2021.0201
Lamm, A. J., & Lamm, K. W. (2019). Using non-probability sampling methods in
agricultural and extension education research. Journal of International
Agricultural and Extension Education, 26(1), 52–59.
https://doi:10.5191/jiaee.2019.26105
Lancaster, K. (2017). Confidentiality, anonymity, and power relations in elite
interviewing: Conducting qualitative policy research in a politicized domain.
International Journal of Social Research Methodology, 20(1), 93–103.
https://doi.org/10.1080/13645579.2015.1123555
Larki, A., Tahmasebi, R., & Reisi, M. (2018). Factors predicting self-care behaviors
among low health literacy hypertensive patients based on health belief model in
Bushehr District, South of Iran. International Journal of Hypertension,
https://doi.org/10.1155/2018/9752736
Lemon, L. L., & Hayes, J. (2020). Enhancing trustworthiness of qualitative findings:
Using Leximancer for qualitative data analysis triangulation. The Qualitative
Report, 25(3), 604–614. https://doi.org/10.46743/2160-3715/2020.4222
Lester, J. N., Cho, Y., & Lochmiller, C. R. (2020). Learning to do qualitative data
analysis: A starting point. Human Resource Development Review, 19(1), 94–106.
https://doi.org/10.1177/1534484320903890
Levine, R., Javalkar, K., Nazareth, M., Faldowski, R. A., de Ferris, M. D. G., Cohen, S.,
Cuttance, J., Hooper, S. R., & Rak, E. (2018). Disparities in health literacy and healthcare
123
utilization among adolescents and young adults with chronic or endstage kidney disease.
Journal of Pediatric Nursing, (38), 57–61.
https://doi.org/10.1016/j.pedn.2017.10.008
Liao, H., & Hitchcock, J. (2018). Reported credibility techniques in higher education
evaluation studies that use qualitative methods: A research synthesis. Evaluation
and Program Planning, 68, 157–165.
https://doi.org/10.1016/j.evalprogplan.2018.03.005
Lincoln, Y. S., & Guba, E. G. (1985). Nonrealistic inquiry. Sage.
Lincoln, Y. S., & Guba, E. G. (1986). But is it rigorous? Trustworthiness and authenticity
in naturalistic evaluation. New directions for program evaluation, 1986(30),
73–84. https://doi.org/10.1002/ev.1427
Linnenluecke, M. K., Marrone, M., & Singh, A. K. (2020). Conducting systematic
literature reviews and bibliometric analyses. Australian Journal of Management,
45(2), 175–194. https://doi.org/10.1177/0312896219877678
Löhr, K., Weinhardt, M., & Sieber, S. (2020). The “world café” as a participatory method
for collecting qualitative data. International Journal of Qualitative Methods, 19,
https://doi.org/10.1177/1609406920916976
Louis, J. P. (2019). Exploring constructs of the health belief model as predictors to
Haitian men’s intention to screen for prostate cancer. Urologic Nursing, 39(2),
72–82. https://doi.org/10.7257/1053-816x.2019.39.2.72
Lowe, A., Norris, A. C., Farris, A. J., & Babbage, D. R. (2018). Quantifying thematic
saturation in qualitative data analysis. Field Methods, 30(3), 191–207.
https://doi.org/10.1177/1525822X17749386

124
Lowe, N. K. (2019). What is a pilot study? Journal of Obstetric, Gynecologic & Neonatal
Nursing, 48(2), 117–118. https://doi.org/10.1016/j.jogn.2019.01.005
Lu, T., & Franklin, A. L. (2018). A Protocol for identifying and sampling from proxy
populations. Social Science Quarterly, 99(4), 1535–1546.
https://doi.org/10.1111/ssqu.12519
Luquis, R. R., & Kensinger, W. S. (2019). Applying the health belief model to assess
prevention services among young adults, International Journal of Health
Promotion and Education, 57(1), 37–47.
https://doi.org/10.1080/14635240.2018.1549958
Lyford, S., & Lash, T. A. (2019). America’s healthcare cost crisis: As the costs of U.S.
healthcare continue to escalate, three commonsense reforms could reverse this
unsustainable trend. Generations, 43(4), 7–12.
https://healthcostcrisis.org/resources.html
MacLeod, S., Musich, S., Gulyas, S., Cheng, Y., Tkatch, R., Cempellin, D., Bhattarai, G.
R., Hawkins, K., & Yeh, C. S. (2017). The impact of inadequate health literacy on
patient satisfaction, healthcare utilization, and expenditures among older adults.
Geriatric Nursing, 38(4), 334–341.
https://doi.org/10.1016/j.gerinurse.2016.12.003
Maher, C., Hadfield, M., Hutchings, M., & de Eyto, A. (2018). Ensuring rigor in
qualitative data analysis: A design research approach to coding combining NVivo
with traditional materials methods. International Journal of Qualitative Methods,
17(1), 1–13. https://doi.org/10.1177/1609406918786362
125
Mallon, S., & Elliott, I. (2019). The emotional risks of turning stories into data: An
exploration of the experiences of qualitative researchers working on sensitive topics.
Societies, 9(3), 62. https://www.mdpi.com/2075-4698/9/3/62
Manson, S. M. (2001). Simplifying complexity: a review of complexity theory.
Geoforum, 32(3), 405–414.
https://doi.org/10.1016/S0016-7185(00)00035-X
Manti, S., & Licari, A. (2018). How to obtain informed consent for research.
Breathe, 14(2), 145–152. https://doi.org/10.1183/20734735.001918
Marshall, M. N. (1996). Sampling for qualitative research. Family Practice, 13(6),
522–526. https://doi.org/10.1093.fampra/13.6.522
Martos-Cabrera, M. B., Gómez-Urquiza, J. L., Cañadas-González, G., Romero-Bejar, J.
L., Suleiman-Martos, N., Cañadas-De la Fuente, G. A., & Albendín-García, L.
(2021, July). Nursing-intense health education intervention for persons with type
2 diabetes: A Quasi-Experimental Study. In Healthcare 9(7), 832
https://doi.org/10.3390/healthcare9070832
McGinley, S., Wei, W., Zhang, L., & Zheng, Y. (2021). The state of qualitative research in
hospitality: A 5-year review 2014 to 2019. Cornell Hospitality
Quarterly, 62(1), 8–20. https://doi.org/10.177/1938965520940294
McGrath, C., Palmgren, P. J., & Liljedahl, M. (2019). Twelve tips for conducting
qualitative research interviews. Medical Teacher, 41(9), 1002–1006.
https://doi.org/10.1080/0142159X.2018.1497149
126
McLean, M. J., Madden, S., & Pressgrove, G. (2021). Complexity theory as a new lens
for digital social advocacy. Public Relations Review, 47(3), Article e102056.
https://doi.org/10.1016/j.pubrev.2021.102056
Merriam, S. B., & Grenier, R. S. (Eds.). (2019). Qualitative research in practice:
Examples for discussion and analysis. John Wiley & Sons.
Michou, M., Panagiotakos, D. B., & Costarelli, V. (2018). Low health literacy and excess
body weight: A systematic review. Central European Journal of Public
Health, 26(3), 234–241. https://doi.org/10.21101/cejph.a5172
Miles, M. B., & Huberman, A. M. (1994). Qualitative data analysis: An expanded
sourcebook. Sage.
Mitchell, E. M. (2020). Concentration of health expenditures and selected characteristics
of high spenders, U.S. civilian noninstitutionalized population, 2017. (Statistical
Brief No. 528). Agency for Healthcare Research and
Quality. https://meps.ahrq.gov/data_files/publications/st528/stat528.shtml
Mohebbi, B., Tol, A., Sadeghi, R., Mohtarami, S. F., & Shamshiri, A. (2019). Self
management intervention program based on the health belief model among women
with gestational diabetes mellitus: a quasi-experimental study. Archives of
Iranian Medicine, 22(4), 168–173.
https://www.proquest.com/scholarly-journals/self-management-
interventionprogram-based-on/docview/2351551362/se-2

127
Moon, M. D. (2019). Triangulation: A method to increase validity, reliability, and
legitimation in clinical research. Journal of Emergency Nursing, 45(1), 103–105.
https://doi.org/10.1016.jen.2018.11.004
Morgan, D. J., Dhruva, S. S., Wright, S. M., & Korenstein, D. (2019). 2019 update on
medical overuse: A systematic review. Journal of American Medical Association
Internal Medicine, 176 (11),
1568–1574. https://doi.org/10.1001/jamainternmed.2019.3842
Moser, A., & Korstjens, I. (2018). Series: Practical guidance to qualitative research. Part
3: Sampling, data collection, and analysis. European Journal of
General
Practice, 24(1), 9–18. https://doi.org/10.1080/13814788.2017.1375091 Motulsky,
S. L. (2021). Is member checking the gold standard of quality in qualitative
research? Qualitative Psychology, 8(3), 389–406.
https://doi.org/10.1037/qup0000215
Muthanna, A. (2019). Critical qualitative inquiry and methodological awareness: The
effectiveness of face-to-face interviews in changing/enhancing participants' beliefs and
practices. International Journal of Research, 8(2), 59–66.
https://doi.org/10.5861/ijrse.2019.3027
National Academies of Sciences, Engineering, and Medicine. (2018). Health-care
utilization as a proxy in disability determination.
https://doi.org/10.17226/24969
128
National Commission for the Protection of Human Subjects and Biomedical and
Behavioral Research. (1979). The Belmont Report: Ethical principles and
guidelines for the protection of human subjects of research. U.S. Department of
Health and Human Services.
National Institutes of Health. (2014). Clear communication: Health literacy.
http://www.nih.gov/clearcommunication/healthliteracy.htm
Nutbeam, D. (2008). The evolving concept of health literacy. Social Science &
Medicine, 67(12), 2072–2078. https://doi.org/10.1016/j.socscimed.2008.09.050
Nutbeam, D., Levin-Zamir, D., & Rowlands, G. (2018b). Health literacy and health
promotion in context. Global Health Promotion, 25(4), 3–5.
https://doi.org/10.1177/1757975918814436
Nutbeam, D., McGill, B., & Premkumar, P. (2018a). Improving health literacy in
community populations: a review of progress. Health Promotion
International, 33(5), 901–911. https://doi.org/10.1093/heapro/dax015
Okan, O., Lopes, E., Bollweg, T. M., Bröder, J., Messer, M., Bruland, D., Bond, E.,
Carvalho, G. S., Sørensen, K., Saboga-Nunes, L., Levin-Zamir, D., Sahrai, D.,
Bittlingmayer, U. H., Pelikan, J. M., Tomas, M., Bauer, U., & Pinheiro, P. (2018).
Generic health literacy measurement instruments for children and adolescents: a
systematic review of the literature. BMC Public Health, 18(1),
1–19. https://doi.org/10.1186/s12889-018-5054-0
Ospina, S. M., Esteve, M., & Lee, S. (2017). Assessing qualitative studies in public
administration Research. Public Administration Review, 78(4), 593–605.

129
https://doi.org/10.1111/puar.12837
O'Sullivan, E., Rassel, G., Berner, M., & Taliaferro, J. (2016). Research methods for
public administrators. Routledge.
Paakkari, L., & Okan, O. (2019). Health literacy—Talking the language of (school)
education. Health Literacy Research and Practice, 3(3), e161–e164.
https://doi.org/10.3928/24748307-20190502-01
Paakkari, L., Torppa, M., Mazur, J., Boberova, Z., Sudeck, G., Kalman, M., & Paakkari,
O. (2020). A comparative study on adolescents' health literacy in Europe: Findings
from the HBSC Study. International Journal of Environmental Research and
Public Health. (17)10, 3543. https://doi.org/10.3390/ijerph17103543
Palumbo, R. (2017). Examining the impacts of health literacy on healthcare costs. An
evidence synthesis. Health Services Management Research, 30(4), 197–212.
https://doi.org/10.1177/0951484817733366
Parker, R. M., & Ratzan, S. (2019). Re-enforce, not re-define health literacy—moving
forward with health literacy 2.0. Journal of Health Communication, 24(12),
923–925. https://doi.org/10.1080/10810730.2019.1691292
Pascale, R. T. (n.d.). Surfing the edge of chaos. Creative Management and
Development, 235-250. https://doi.org/10.4135/9781446213704.n18
Pelikan, J. M., Ganahl, K., & Roethlin, F. (2018). Health literacy as a determinant,
mediator and/or moderator of health: empirical models using the European health
literacy survey dataset. Global Health Promotion, 25(4), 57–66.
https://doi.org/10.1177/1757975918788300
130
Philippi, J., & Lauderdale, J. (2018). A Guide to field notes for qualitative research:
context and conversation. Qualitative Health Research, 28(3), 381–388.
https://doi.org/10.1177/1049732317697102
Pleasant, A., O’Leary, C., & Carmona, R. (2020). Health literacy: Global advances with a
focus upon the Shanghai declaration on promoting health in the 2030 agenda for
sustainable development. Information Services & Use, 40(1–2), 3–16.
https://doi.org/10.3233/ISU-200080
Prince, L. Y., Schmidtke, C., Beck, J. K., & Hadden, K. B. (2018). An assessment of
organizational health literacy practices at an academic health center. Quality
Management in Health Care, 27(2), 93–97.
https://doi.org/10.1097/QMH.0000000000000162
Rademakers, J., & Heijmans, M. (2018). Beyond reading and understanding: Health
literacy as the capacity to act. International Journal of Environmental Research and
Public Health, 15(8), 1676. https://doi.org/10.3390/ijerph15081676
Ratzan, S. C., & Parker, R. M. (2000). Health literacy. National library of medicine
current bibliographies in medicine: National Institutes of Health, US Department
of Health, and Human Services.
https://www.nlm.nih.gov/pubs/resources.html
Reinhart, R. M., Fink, A., Bhattarai, S., Cheng, J. J., Saha, A., Worten, K., Cronin, J., &
Shah, R. (2022). Engagement and bundle compliance during COVID-19: A virtual
strategy. Pediatric Quality & Safety, 7(2), e540.
https://doi.org/10.1097/pq9.0000000000000540
131
Rimer, B. K., & Glanz, K. (2005). Theory at a glance: A guide for health promotion
practice (2nd ed,). U.S. Department of Health and Human Services, National
Institutes of Health, National Cancer Institute.
Roberts, R. E. (2020). Qualitative interview questions: Guidance for novice researchers.
The Qualitative Report, 25(9), Article 1.
https://doi.org/10.46743/2160-3715/2020.4640
Roberts, T., Esponda, G. M., Krupchanka, D., Shidhaye, R., Patel, V., & Rathod, S.
(2018). Factors associated with health service utilization for common mental
disorders: a systematic review. BMC Psychiatry, 18(1), 1–19.
https://do.org/10.1186/s12888-018-1837-1
Rose, J., & Johnson, C. W. (2020). Contextualizing reliability and validity in qualitative
research: toward more rigorous and trustworthy qualitative social science in
leisure research. Journal of Leisure Research, 51(4), 432–451.
https://doi.org/10.1080/00222216.2020.1722042
Rosenhead, J., Franco, L. A., Grint, K., & Friedland, B. (2019). Complexity theory and
leadership practice: A review, a critique, and some recommendations. The
Leadership Quarterly, 30(5), Article e101304.
https://doi.org/10.1016/j.leaqua.2019.07.002
Rosenstock, I. M. (1966). “Why people use health services.” Milbank Memorial Fund
Quarterly 44, 94–127. https://doi.org/10.2307/3348967.
Rosenstock, I. M. (1974). Historical origins of the health belief model. Health Education
Monographs, 2(4), 328–335. https://doi.org/10.1177/109019817400200405
132
Rutberg, S., & Bouikidis, C. D. (2018). Focusing on the fundamentals: A simplistic
differentiation between qualitative and quantitative research. Nephrology Nursing
Journal, 45(2), 209–213. https://www.annanurse.org
Sadeghi, R., Hashemi, M., & Khanjani, N. (2018). The impact of educational intervention
based on the health belief model on observing standard precautions among emergency
center nurses in Sirjan, Iran. Health Education Research, 33(4),
327–335. https://doi.org/10.1093/her/cyy020
Saso, A., Skirrow, H., & Kampmann, B. (2020). Impact of COVID-19 on immunization
services for maternal and infant vaccines: Results of a survey conducted by
imprint—the immunizing pregnant women and infants’ network. Vaccines, 8(3),
556. https://doi.org/10.3390/vacines8030556
Saunders, M., Lewis, P., & Thornhill, A. (2019). Research methods for business students
(8th ed.). Pearson Education Limited.
Scherzinger, G., & Bobbert, M. (2017). Evaluation of research ethics committees:
Criteria for the ethical quality of the review process. Accountability in research,
24(3), 152-176. https://doi.org/10.1080/08989621.2016.1273778 Schillinger, D.
(2021). Social Determinants, Health Literacy, and Disparities:
Intersections and controversies. Health Literacy Research and Practice, 5(3).
234–243. https://doi.org/10.3928/24748307-20210712-01
Schneider, M., & Somers, M. (2006). Organizations as complex adaptive systems:
Implications of complexity theory for leadership research. The Leadership

133
Quarterly, 17(4), 351–365. https://doi.org/10.1016/j.leaqua.2006.04.006
Schwartzberg, J. G., Vangeest, J. B., & Wang, C. C. (Eds.). (2005). Understanding health
literacy: Implications for medicine and public health. American Medical Association,
69–84. https://doi.org/10.1111/j.1525-1497.2006.00547.x
Secretary’s Advisory Committee on National Health Promotion and Disease Prevention
objectives for 2030. (2019). History of health literacy definition. Healthy People
2030. https://health.gov/healthypeople/priority-areas/health-literacy-
healthypeople-2030/history-health-literacy-definitions
Sentell, T., Vamos, S., & Okan, O. (2020). Interdisciplinary perspectives on health
literacy research around the world: More important than ever in a time of
COVID-19. International Journal of Environmental Research and Public
Health, 17(9). 3010, https://doi:10.3390/ijerph17093010
Shao, S., Wang, M., Jin, G., Zhao, Y., Lu, X., & Du, J. (2018). Analysis of health service
utilization of migrants in Beijing using Andersen health service utilization model.
BMC health Services Research, 18(1), 1–11.
https://doi.org/10.1186/s12913-018-3271-y
Sharma, M. (2021). Theoretical foundations of health education and health promotion.
Jones & Bartlett Learning.
Sheppard, J., & Thomas, C. B. (2021). Community pharmacists and communication in
the time of COVID-19: Applying the health belief model. Research in Social and
Administrative Pharmacy, 17(1), 1984–1987.
https://doi.org/10.1016/j.sapharm.2020.03.017
134
Shrank, W. H., Rogstad, T. L., & Parekh, N. (2019). Waste in the U.S. healthcare
system: Estimated costs and potential for savings. Journal of American Medical
Association, 322(15), 1501–1509. https://doi.org/10.1001/jama.2019.13978
Simon, M. K. (2011). Dissertation and scholarly research: Recipes for success
(2011 Ed.). Dissertation Success, LLC. https://www.dissertationredicpes.com
Simonds, S. K. (1974). Health education as social policy. Health Education
Monographs, 2(1_suppl), 1–10. https://doi.org/10.1177/10901981740020S102
Simpson, R. M., Knowles, E., & O’Cathain, A. (2020). Health literacy levels of British
adults: A cross-sectional survey using two domains of the health literacy questionnaire.
BMC Public Health, 20, 1–13.
http://doi.org/10.1186/s12889-020-09727-w
Sisko, A. M., Keehan, S. P., Poisal, J. A., Cuckler, G. A., Smith, S. D., Madison, A. J.,
Rennie, K. E., & Hardesty, J. C. (2019). National health expenditure projections,
2018-2027 economic and demographic trends drive spending and enrollment
growth. Health Affairs, 38(3), 491–501. https://doi.org/10.1377/hlthaff.2018.05499
Skinner, C. S., Tiro, J., & Champion, V. L. (2015). Background on the health belief
model. Health behavior: Theory, Research, and Practice, 75–91.
SoleimanvandiAzar, N., Kamal, S. H. M., Sajjadi, H., Harouni, G. G., Karimi, S. E.,
Djalalinia, S., & Forouzan, A. S. (2020). Determinants of outpatient health service
utilization according to Andersen’s behavioral model: A systematic scoping review.
Iranian Journal of Medical Sciences, 45(6), 405–424.
https://doi.org/10.30476/ijms.2020.85028.1481
135
Sørensen, K., & Pleasant, A. (2017). Understanding the conceptual importance of the
differences among health literacy definitions. Studies in Health Technology and
Informatics, 240, 3–14. https://doi.org/10.3233/978-1-61499-790-0-3
Spoor, B., & Rothman, M. (2021). On the critical utility of complexity theory in
intelligence studies. Intelligence & National Security, 36(4), 555–568.
https://doi.org/10.1080/02684527.2021.1893076
Stenfors, T., Kajamaa, A., & Bennett, D. (2020). How to assess the quality of
qualitative research. The Clinical Teacher, 17(6), 596–599.
https://doi.org/10.111/tct.13242
Stielke, A., Dyakova, M., Ashton, K., & van Dam, T. (2019). The social and economic
benefit of health literacy interventions in the WHO EURO region. European
Journal of Public Health, 29(Supplement_4), 186–390.
https://doi.org/10.1093/eurpub.ckz186.390
Svendsen, M. T., Bak, C. K., Sørensen, K., Pelikan, J., Riddersholm, S. J., Skals, R. K.,
Mortensen, R. N., Maindal, H. T., Boggild, H., Nielsen, G., & Torp-Pedersen, C.
(2020). Associations of health literacy with socioeconomic position, health risk
behavior, and health status: a large national population-based survey among
Danish adults. BMC Public Health 20(1), 1–12.
https://doi.org/10.1186/s12889-020-08498-8
Theofanidis, D., & Fountouki, A. (2018). Limitations and delimitations in the research
process. Perioperative Nursing-Quarterly scientific, online official journal of
GORNA, 7(3), 155–163. https://doi.org/10.5281/zenodo.2552022

136
Trezona, A., Rowlands, G., & Nutbeam, D. (2018). Progress in implementing national
policies and strategies for health literacy—what have we learned so
far? International Journal of Environmental Research and Public Health, 15(7),
1–17. https://doi.org/10.3390/ijerph15071554
Turner, J. R., & Baker, R. M. (2019). Complexity Theory: An overview with potential
applications for the social sciences. Systems, 7(1), 4.
http://doi.org/10.3390/systems7010004
Tyrer, S., & Heyman, B. (2016). Sampling in epidemiological research: Issues, hazards,
and pitfalls. British Journal of Psychiatry Bulletin, 40, 57–60.
https://doi.org/10.1192/pb.bp.114.050203
Uemura, K., Yamada, M., & Okamoto, H. (2018). Effects of active learning on health
literacy and behavior in older adults: a randomized controlled trial. Journal of the
American Geriatrics Society, 66(9), 1721–1729.
https://doi.org/10.1111/jgs.15458
Vahedian-Shahroodi, M., Tehrani, H., Robat-Sarpooshi, D., GHolian–Aval, M., Jafari,
A., & Alizadeh-Siuki, H. (2021). The impact of health education on nutritional
behaviors in female students: An application of health belief model. International
Journal of Health Promotion and Education, 59(2), 70–82.
https://doi.org/10.1080/14635240.2019.1696219
Van Diepen, S., Tran, D. T., Ezekowitz, J. A., Zygun, D. A., Katz, J. N., Lopes, R. D.,
Newby, L. K., McAllister, F. A., & Kaul, P. (2018). The high cost of critical care unit
over-utilization for patients with NSTE acute coronary syndrome. American
137
Heart Journal, (202), 84–88. https://doi.org/10.1016/j.ahj.2018.05.003
Van Wyk, J., Bothma, T., & Holmner, M. (2020). "A conceptual virtual research
environment model for the management of research data, a South African perspective,"
Library Management, 4 (6/7), 417–446.
https://doi.org/10.1108/LM-02-2020-0037
Varpio, L., Ajjawi, R., Monrouxe, L. V., O’Brien, B. C., & Rees, C. E. (2017). Shedding
the cobra effect: Problematizing thematic emergence, triangulation, saturation, and
member checking. Medical Education, 51(1), 40–50.
https://doi.org/10.1111/medu.13124
Varpio, L., Young, M., Uijtdehaage, S., & Paradis, E. (2019). The distinctions between
theory, theoretical framework, and conceptual framework. Academic Medicine.
95(7), 989–994. https://doi.org/10.1097/acm.0000000000003075
Walters, R., Leslie, S. J., Polson, R., Cusack, T., & Gorely, T. (2020). Establishing the
efficacy of interventions to improve health literacy and health behaviors: A
systematic review. BMC Public Health, 20(1), 1–17.
https://doi.org/10.1186/s12889-020-08991-0
Williams, M., & Moser, T. (2019). The art of coding and thematic exploration in
qualitative research. International Management Review, 15(1), 45–55.
https://www.imrjournal.org
World Health Organization. (2017). Shanghai declaration on promoting health in the
2030 agenda for sustainable development. Health Promotion International, (3),
7–8. https://doi.org/10.1093/heapro/daw103
138
World Health Organization. (2020). Pulse survey on continuity of essential health
services during the COVID-19 Pandemic: Interim Report. 1–21
https://www.who.int/publications/i/item/WHO-2019-nCoV-EHS_continuitysurvey-
2020.1
Yeong, M. L., Ismail, R., Ismail, N. H., & Hamzah, M. I. (2018). Interview protocol
refinement: Fine-tuning qualitative research interview questions for multi-racial
populations in Malaysia. The Qualitative Report, (23)11, 2700–2713
https://doi.org/10.46743/2160-3715/2018.3412
Yin, R. K. (2018). Case study research and application: Design and methods (6th ed.).
Sage Publications.
Young, J. C., Rose, D. C., Mumby, H. S., Benitez‐Capistros, F., Derrick, C. J., Finch,
T., Garcia, C., Home, C., Marwaha, E., Morgans, C., Parkinson, S., Shah, J., Wilson,
K. A., & Mukherjee, N. (2018). A methodological guide to using and reporting on
interviews in conservation science research. Methods in Ecology and Evolution,
9(1), 10–19. https://doi.org/10.1111/204-210X.12828
Zheng, M., Jin, H., Shi, N., Duan, C., Wang, D., Yu, X., & Li, X. (2018). The relationship
between health literacy and quality of life: A systematic review and meta-analysis.
Health and Quality of Life Outcomes, 16(1), 1–10.
https://doi.org/10.1186/s12955-018-1031-7
Zheng, Z., Han, X., Zhao, J., Banegas, M. P., Tucker-Seeley, R., Rai, A., Fedewa, S. A.,
Song, W., Jemal, A., & Yabroff, K. R. (2020a). Financial hardship, healthcare
utilization, and health among US cancer survivors. American Journal of

139
Preventive Medicine, 59(1), 68–78.
https://doi.org/10.1016/j.amepre.2020.02.016
Zheng, Z., Jemal, A., Tucker-Seeley, R., Banegas, M. P., Han, X., Rai, A., Zhao, J., &
Yabroff, K. R. (2020b). Worry about daily financial needs and food insecurity
among cancer survivors in the United States. Journal of the National
Comprehensive Cancer Network, 18(3), 315–327.
https://doi.org/10.6004/jnccn.2019.7359
Mitchell, E. M. (2020). Concentration of health expenditures and selected
characteristics of high spenders, U.S. civilian noninstitutionalized population,
2017. (Statistical
Brief No. 528). Agency for Healthcare Research and
Quality. https://meps.ahrq.gov/data_files/publications/st528/stat528.shtml
Mohebbi, B., Tol, A., Sadeghi, R., Mohtarami, S. F., & Shamshiri, A. (2019). Self
management intervention program based on the health belief model among women
with gestational diabetes mellitus: a quasi-experimental study. Archives of
Iranian Medicine, 22(4), 168–173.
https://www.proquest.com/scholarly-journals/self-management-
interventionprogram-based-on/docview/2351551362/se-2
Moon, M. D. (2019). Triangulation: A method to increase validity, reliability, and
legitimation in clinical research. Journal of Emergency Nursing, 45(1), 103–105.
https://doi.org/10.1016.jen.2018.11.004
140
Morgan, D. J., Dhruva, S. S., Wright, S. M., & Korenstein, D. (2019). 2019 update on
medical overuse: A systematic review. Journal of American Medical Association
Internal Medicine, 176 (11),
1568–1574. https://doi.org/10.1001/jamainternmed.2019.3842
Moser, A., & Korstjens, I. (2018). Series: Practical guidance to qualitative research. Part
3: Sampling, data collection, and analysis. European Journal of
General
Practice, 24(1), 9–18. https://doi.org/10.1080/13814788.2017.1375091 Motulsky,
S. L. (2021). Is member checking the gold standard of quality in qualitative
research? Qualitative Psychology, 8(3), 389–406.
https://doi.org/10.1037/qup0000215
Muthanna, A. (2019). Critical qualitative inquiry and methodological awareness: The
effectiveness of face-to-face interviews in changing/enhancing participants' beliefs and
practices. International Journal of Research, 8(2), 59–66.
https://doi.org/10.5861/ijrse.2019.3027
National Academies of Sciences, Engineering, and Medicine. (2018). Health-care
utilization as a proxy in disability determination.
https://doi.org/10.17226/24969
National Commission for the Protection of Human Subjects and Biomedical and
Behavioral Research. (1979). The Belmont Report: Ethical principles and
guidelines for the protection of human subjects of research. U.S. Department of
Health and Human Services.
141
National Institutes of Health. (2014). Clear communication: Health literacy.
http://www.nih.gov/clearcommunication/healthliteracy.htm
Nutbeam, D. (2008). The evolving concept of health literacy. Social Science &
Medicine, 67(12), 2072–2078. https://doi.org/10.1016/j.socscimed.2008.09.050
Nutbeam, D., Levin-Zamir, D., & Rowlands, G. (2018b). Health literacy and health
promotion in context. Global Health Promotion, 25(4), 3–5.
https://doi.org/10.1177/1757975918814436
Nutbeam, D., McGill, B., & Premkumar, P. (2018a). Improving health literacy in
community populations: a review of progress. Health Promotion
International, 33(5), 901–911. https://doi.org/10.1093/heapro/dax015
Okan, O., Lopes, E., Bollweg, T. M., Bröder, J., Messer, M., Bruland, D., Bond, E.,
Carvalho, G. S., Sørensen, K., Saboga-Nunes, L., Levin-Zamir, D., Sahrai, D.,
Bittlingmayer, U. H., Pelikan, J. M., Tomas, M., Bauer, U., & Pinheiro, P. (2018).
Generic health literacy measurement instruments for children and adolescents: a
systematic review of the literature. BMC Public Health, 18(1),
1–19. https://doi.org/10.1186/s12889-018-5054-0
Ospina, S. M., Esteve, M., & Lee, S. (2017). Assessing qualitative studies in public
administration Research. Public Administration Review, 78(4), 593–605.
https://doi.org/10.1111/puar.12837
O'Sullivan, E., Rassel, G., Berner, M., & Taliaferro, J. (2016). Research methods for
public administrators. Routledge.

142
Paakkari, L., & Okan, O. (2019). Health literacy—Talking the language of (school)
education. Health Literacy Research and Practice, 3(3), e161–e164.
https://doi.org/10.3928/24748307-20190502-01
Paakkari, L., Torppa, M., Mazur, J., Boberova, Z., Sudeck, G., Kalman, M., & Paakkari,
O. (2020). A comparative study on adolescents' health literacy in Europe: Findings
from the HBSC Study. International Journal of Environmental Research and
Public Health. (17)10, 3543. https://doi.org/10.3390/ijerph17103543
Palumbo, R. (2017). Examining the impacts of health literacy on healthcare costs. An
evidence synthesis. Health Services Management Research, 30(4), 197–212.
https://doi.org/10.1177/0951484817733366
Parker, R. M., & Ratzan, S. (2019). Re-enforce, not re-define health literacy—moving
forward with health literacy 2.0. Journal of Health Communication, 24(12),
923–925. https://doi.org/10.1080/10810730.2019.1691292
Pascale, R. T. (n.d.). Surfing the edge of chaos. Creative Management and
Development, 235-250. https://doi.org/10.4135/9781446213704.n18
Pelikan, J. M., Ganahl, K., & Roethlin, F. (2018). Health literacy as a determinant,
mediator and/or moderator of health: empirical models using the European health
literacy survey dataset. Global Health Promotion, 25(4), 57–66.
https://doi.org/10.1177/1757975918788300
Philippi, J., & Lauderdale, J. (2018). A Guide to field notes for qualitative research:
context and conversation. Qualitative Health Research, 28(3), 381–388.
https://doi.org/10.1177/1049732317697102
143
Pleasant, A., O’Leary, C., & Carmona, R. (2020). Health literacy: Global advances with a
focus upon the Shanghai declaration on promoting health in the 2030 agenda for
sustainable development. Information Services & Use, 40(1–2), 3–16.
https://doi.org/10.3233/ISU-200080
Prince, L. Y., Schmidtke, C., Beck, J. K., & Hadden, K. B. (2018). An assessment of
organizational health literacy practices at an academic health center. Quality
Management in Health Care, 27(2), 93–97.
https://doi.org/10.1097/QMH.0000000000000162
Rademakers, J., & Heijmans, M. (2018). Beyond reading and understanding: Health
literacy as the capacity to act. International Journal of Environmental Research and
Public Health, 15(8), 1676. https://doi.org/10.3390/ijerph15081676
Ratzan, S. C., & Parker, R. M. (2000). Health literacy. National library of medicine
current bibliographies in medicine: National Institutes of Health, US Department
of Health, and Human Services.
https://www.nlm.nih.gov/pubs/resources.html
Reinhart, R. M., Fink, A., Bhattarai, S., Cheng, J. J., Saha, A., Worten, K., Cronin, J., &
Shah, R. (2022). Engagement and bundle compliance during COVID-19: A virtual
strategy. Pediatric Quality & Safety, 7(2), e540.
https://doi.org/10.1097/pq9.0000000000000540
Rimer, B. K., & Glanz, K. (2005). Theory at a glance: A guide for health promotion
practice (2nd ed,). U.S. Department of Health and Human Services, National
Institutes of Health, National Cancer Institute.
Roberts, R. E. (2020). Qualitative interview questions: Guidance for novice researchers.

144
The Qualitative Report, 25(9), Article 1.
https://doi.org/10.46743/2160-3715/2020.4640
Roberts, T., Esponda, G. M., Krupchanka, D., Shidhaye, R., Patel, V., & Rathod, S.
(2018). Factors associated with health service utilization for common mental
disorders: a systematic review. BMC Psychiatry, 18(1), 1–19.
https://do.org/10.1186/s12888-018-1837-1
Rose, J., & Johnson, C. W. (2020). Contextualizing reliability and validity in qualitative
research: toward more rigorous and trustworthy qualitative social science in
leisure research. Journal of Leisure Research, 51(4), 432–451.
https://doi.org/10.1080/00222216.2020.1722042
Rosenhead, J., Franco, L. A., Grint, K., & Friedland, B. (2019). Complexity theory and
leadership practice: A review, a critique, and some recommendations. The
Leadership Quarterly, 30(5), Article e101304.
https://doi.org/10.1016/j.leaqua.2019.07.002
Rosenstock, I. M. (1966). “Why people use health services.” Milbank Memorial Fund
Quarterly 44, 94–127. https://doi.org/10.2307/3348967.
Rosenstock, I. M. (1974). Historical origins of the health belief model. Health Education
Monographs, 2(4), 328–335. https://doi.org/10.1177/109019817400200405
Rutberg, S., & Bouikidis, C. D. (2018). Focusing on the fundamentals: A simplistic
differentiation between qualitative and quantitative research. Nephrology Nursing
Journal, 45(2), 209–213. https://www.annanurse.org
145
Sadeghi, R., Hashemi, M., & Khanjani, N. (2018). The impact of educational intervention
based on the health belief model on observing standard precautions among emergency
center nurses in Sirjan, Iran. Health Education Research, 33(4),
327–335. https://doi.org/10.1093/her/cyy020
Saso, A., Skirrow, H., & Kampmann, B. (2020). Impact of COVID-19 on immunization
services for maternal and infant vaccines: Results of a survey conducted by
imprint—the immunizing pregnant women and infants’ network. Vaccines, 8(3),
556. https://doi.org/10.3390/vacines8030556
Saunders, M., Lewis, P., & Thornhill, A. (2019). Research methods for business students
(8th ed.). Pearson Education Limited.
Scherzinger, G., & Bobbert, M. (2017). Evaluation of research ethics committees:
Criteria for the ethical quality of the review process. Accountability in research,
24(3), 152-176. https://doi.org/10.1080/08989621.2016.1273778 Schillinger, D.
(2021). Social Determinants, Health Literacy, and Disparities:
Intersections and controversies. Health Literacy Research and Practice, 5(3).
234–243. https://doi.org/10.3928/24748307-20210712-01
Schneider, M., & Somers, M. (2006). Organizations as complex adaptive systems:
Implications of complexity theory for leadership research. The Leadership
Quarterly, 17(4), 351–365. https://doi.org/10.1016/j.leaqua.2006.04.006
Schwartzberg, J. G., Vangeest, J. B., & Wang, C. C. (Eds.). (2005). Understanding health
literacy: Implications for medicine and public health. American Medical Association,
69–84. https://doi.org/10.1111/j.1525-1497.2006.00547.x
146
Secretary’s Advisory Committee on National Health Promotion and Disease Prevention
objectives for 2030. (2019). History of health literacy definition. Healthy People
2030. https://health.gov/healthypeople/priority-areas/health-literacy-
healthypeople-2030/history-health-literacy-definitions
Sentell, T., Vamos, S., & Okan, O. (2020). Interdisciplinary perspectives on health
literacy research around the world: More important than ever in a time of
COVID-19. International Journal of Environmental Research and Public
Health, 17(9). 3010, https://doi:10.3390/ijerph17093010
Shao, S., Wang, M., Jin, G., Zhao, Y., Lu, X., & Du, J. (2018). Analysis of health service
utilization of migrants in Beijing using Andersen health service utilization model.
BMC health Services Research, 18(1), 1–11.
https://doi.org/10.1186/s12913-018-3271-y
Sharma, M. (2021). Theoretical foundations of health education and health promotion.
Jones & Bartlett Learning.
Sheppard, J., & Thomas, C. B. (2021). Community pharmacists and communication in
the time of COVID-19: Applying the health belief model. Research in Social and
Administrative Pharmacy, 17(1), 1984–1987.
https://doi.org/10.1016/j.sapharm.2020.03.017
Shrank, W. H., Rogstad, T. L., & Parekh, N. (2019). Waste in the U.S. healthcare
system: Estimated costs and potential for savings. Journal of American Medical
Association, 322(15), 1501–1509. https://doi.org/10.1001/jama.2019.13978
Simon, M. K. (2011). Dissertation and scholarly research: Recipes for success
(2011 Ed.). Dissertation Success, LLC. https://www.dissertationredicpes.com

147
Simonds, S. K. (1974). Health education as social policy. Health Education
Monographs, 2(1_suppl), 1–10. https://doi.org/10.1177/10901981740020S102
Simpson, R. M., Knowles, E., & O’Cathain, A. (2020). Health literacy levels of British
adults: A cross-sectional survey using two domains of the health literacy questionnaire.
BMC Public Health, 20, 1–13.
http://doi.org/10.1186/s12889-020-09727-w
Sisko, A. M., Keehan, S. P., Poisal, J. A., Cuckler, G. A., Smith, S. D., Madison, A. J.,
Rennie, K. E., & Hardesty, J. C. (2019). National health expenditure projections,
2018-2027 economic and demographic trends drive spending and enrollment
growth. Health Affairs, 38(3), 491–501. https://doi.org/10.1377/hlthaff.2018.05499
Skinner, C. S., Tiro, J., & Champion, V. L. (2015). Background on the health belief
model. Health behavior: Theory, Research, and Practice, 75–91.
SoleimanvandiAzar, N., Kamal, S. H. M., Sajjadi, H., Harouni, G. G., Karimi, S. E.,
Djalalinia, S., & Forouzan, A. S. (2020). Determinants of outpatient health service
utilization according to Andersen’s behavioral model: A systematic scoping review.
Iranian Journal of Medical Sciences, 45(6), 405–424.
https://doi.org/10.30476/ijms.2020.85028.1481
Sørensen, K., & Pleasant, A. (2017). Understanding the conceptual importance of the
differences among health literacy definitions. Studies in Health Technology and
Informatics, 240, 3–14. https://doi.org/10.3233/978-1-61499-790-0-3
148
Spoor, B., & Rothman, M. (2021). On the critical utility of complexity theory in
intelligence studies. Intelligence & National Security, 36(4), 555–568.
https://doi.org/10.1080/02684527.2021.1893076
Stenfors, T., Kajamaa, A., & Bennett, D. (2020). How to assess the quality of
qualitative research. The Clinical Teacher, 17(6), 596–599.
https://doi.org/10.111/tct.13242
Stielke, A., Dyakova, M., Ashton, K., & van Dam, T. (2019). The social and economic
benefit of health literacy interventions in the WHO EURO region. European
Journal of Public Health, 29(Supplement_4), 186–390.
https://doi.org/10.1093/eurpub.ckz186.390
Svendsen, M. T., Bak, C. K., Sørensen, K., Pelikan, J., Riddersholm, S. J., Skals, R. K.,
Mortensen, R. N., Maindal, H. T., Boggild, H., Nielsen, G., & Torp-Pedersen, C.
(2020). Associations of health literacy with socioeconomic position, health risk
behavior, and health status: a large national population-based survey among
Danish adults. BMC Public Health 20(1), 1–12.
https://doi.org/10.1186/s12889-020-08498-8
Theofanidis, D., & Fountouki, A. (2018). Limitations and delimitations in the research
process. Perioperative Nursing-Quarterly scientific, online official journal of
GORNA, 7(3), 155–163. https://doi.org/10.5281/zenodo.2552022
Trezona, A., Rowlands, G., & Nutbeam, D. (2018). Progress in implementing national
policies and strategies for health literacy—what have we learned so
far? International Journal of Environmental Research and Public Health, 15(7),
149
1–17. https://doi.org/10.3390/ijerph15071554
Turner, J. R., & Baker, R. M. (2019). Complexity Theory: An overview with potential
applications for the social sciences. Systems, 7(1), 4.
http://doi.org/10.3390/systems7010004
Tyrer, S., & Heyman, B. (2016). Sampling in epidemiological research: Issues, hazards,
and pitfalls. British Journal of Psychiatry Bulletin, 40, 57–60.
https://doi.org/10.1192/pb.bp.114.050203
Uemura, K., Yamada, M., & Okamoto, H. (2018). Effects of active learning on health
literacy and behavior in older adults: a randomized controlled trial. Journal of the
American Geriatrics Society, 66(9), 1721–1729.
https://doi.org/10.1111/jgs.15458
Vahedian-Shahroodi, M., Tehrani, H., Robat-Sarpooshi, D., GHolian–Aval, M., Jafari,
A., & Alizadeh-Siuki, H. (2021). The impact of health education on nutritional
behaviors in female students: An application of health belief model. International
Journal of Health Promotion and Education, 59(2), 70–82.
https://doi.org/10.1080/14635240.2019.1696219
Van Diepen, S., Tran, D. T., Ezekowitz, J. A., Zygun, D. A., Katz, J. N., Lopes, R. D.,
Newby, L. K., McAllister, F. A., & Kaul, P. (2018). The high cost of critical care unit
over-utilization for patients with NSTE acute coronary syndrome. American
Heart Journal, (202), 84–88. https://doi.org/10.1016/j.ahj.2018.05.003
150
Van Wyk, J., Bothma, T., & Holmner, M. (2020). "A conceptual virtual research
environment model for the management of research data, a South African perspective,"
Library Management, 4 (6/7), 417–446.
https://doi.org/10.1108/LM-02-2020-0037
Varpio, L., Ajjawi, R., Monrouxe, L. V., O’Brien, B. C., & Rees, C. E. (2017). Shedding
the cobra effect: Problematizing thematic emergence, triangulation, saturation, and
member checking. Medical Education, 51(1), 40–50.
https://doi.org/10.1111/medu.13124
Varpio, L., Young, M., Uijtdehaage, S., & Paradis, E. (2019). The distinctions between
theory, theoretical framework, and conceptual framework. Academic Medicine.
95(7), 989–994. https://doi.org/10.1097/acm.0000000000003075
Walters, R., Leslie, S. J., Polson, R., Cusack, T., & Gorely, T. (2020). Establishing the
efficacy of interventions to improve health literacy and health behaviors: A
systematic review. BMC Public Health, 20(1), 1–17.
https://doi.org/10.1186/s12889-020-08991-0
Williams, M., & Moser, T. (2019). The art of coding and thematic exploration in
qualitative research. International Management Review, 15(1), 45–55.
https://www.imrjournal.org
World Health Organization. (2017). Shanghai declaration on promoting health in the
2030 agenda for sustainable development. Health Promotion International, (3),
7–8. https://doi.org/10.1093/heapro/daw103
151
World Health Organization. (2020). Pulse survey on continuity of essential health
services during the COVID-19 Pandemic: Interim Report. 1–21
https://www.who.int/publications/i/item/WHO-2019-nCoV-EHS_continuitysurvey-
2020.1
Yeong, M. L., Ismail, R., Ismail, N. H., & Hamzah, M. I. (2018). Interview protocol
refinement: Fine-tuning qualitative research interview questions for multi-racial
populations in Malaysia. The Qualitative Report, (23)11, 2700–2713
https://doi.org/10.46743/2160-3715/2018.3412
Yin, R. K. (2018). Case study research and application: Design and methods (6th ed.).
Sage Publications.
Young, J. C., Rose, D. C., Mumby, H. S., Benitez‐Capistros, F., Derrick, C. J., Finch,
T., Garcia, C., Home, C., Marwaha, E., Morgans, C., Parkinson, S., Shah, J., Wilson,
K. A., & Mukherjee, N. (2018). A methodological guide to using and reporting on
interviews in conservation science research. Methods in Ecology and Evolution,
9(1), 10–19. https://doi.org/10.1111/204-210X.12828
Zheng, M., Jin, H., Shi, N., Duan, C., Wang, D., Yu, X., & Li, X. (2018). The relationship
between health literacy and quality of life: A systematic review and meta-analysis.
Health and Quality of Life Outcomes, 16(1), 1–10.
https://doi.org/10.1186/s12955-018-1031-7
Zheng, Z., Han, X., Zhao, J., Banegas, M. P., Tucker-Seeley, R., Rai, A., Fedewa, S. A.,
Song, W., Jemal, A., & Yabroff, K. R. (2020a). Financial hardship, healthcare
utilization, and health among US cancer survivors. American Journal of

152
Preventive Medicine, 59(1), 68–78.
https://doi.org/10.1016/j.amepre.2020.02.016
Zheng, Z., Jemal, A., Tucker-Seeley, R., Banegas, M. P., Han, X., Rai, A., Zhao, J., &
Yabroff, K. R. (2020b). Worry about daily financial needs and food insecurity
among cancer survivors in the United States. Journal of the National
Comprehensive Cancer Network, 18(3), 315–327.
https://doi.org/10.6004/jnccn.2019.7359
Mitchell, E. M. (2020). Concentration of health expenditures and selected characteristics
of high spenders, U.S. civilian noninstitutionalized population, 2017. (Statistical
Brief No. 528). Agency for Healthcare Research and
Quality. https://meps.ahrq.gov/data_files/publications/st528/stat528.shtml
Mohebbi, B., Tol, A., Sadeghi, R., Mohtarami, S. F., & Shamshiri, A. (2019). Self
management intervention program based on the health belief model among women
with gestational diabetes mellitus: a quasi-experimental study. Archives of
Iranian Medicine, 22(4), 168–173.
https://www.proquest.com/scholarly-journals/self-management-
interventionprogram-based-on/docview/2351551362/se-2
Moon, M. D. (2019). Triangulation: A method to increase validity, reliability, and
legitimation in clinical research. Journal of Emergency Nursing, 45(1), 103–105.
https://doi.org/10.1016.jen.2018.11.004
Morgan, D. J., Dhruva, S. S., Wright, S. M., & Korenstein, D. (2019). 2019 update on
medical overuse: A systematic review. Journal of American Medical Association

153
Internal Medicine, 176 (11),
1568–1574. https://doi.org/10.1001/jamainternmed.2019.3842
Moser, A., & Korstjens, I. (2018). Series: Practical guidance to qualitative research. Part
3: Sampling, data collection, and analysis. European Journal of
General
Practice, 24(1), 9–18. https://doi.org/10.1080/13814788.2017.1375091 Motulsky,
S. L. (2021). Is member checking the gold standard of quality in qualitative
research? Qualitative Psychology, 8(3), 389–406.
https://doi.org/10.1037/qup0000215
Muthanna, A. (2019). Critical qualitative inquiry and methodological awareness: The
effectiveness of face-to-face interviews in changing/enhancing participants' beliefs and
practices. International Journal of Research, 8(2), 59–66.
https://doi.org/10.5861/ijrse.2019.3027
National Academies of Sciences, Engineering, and Medicine. (2018). Health-care
utilization as a proxy in disability determination.
https://doi.org/10.17226/24969
National Commission for the Protection of Human Subjects and Biomedical and
Behavioral Research. (1979). The Belmont Report: Ethical principles and
guidelines for the protection of human subjects of research. U.S. Department of
Health and Human Services.
National Institutes of Health. (2014). Clear communication: Health literacy.
http://www.nih.gov/clearcommunication/healthliteracy.htm
Nutbeam, D. (2008). The evolving concept of health literacy. Social Science &

154
Medicine, 67(12), 2072–2078. https://doi.org/10.1016/j.socscimed.2008.09.050
Nutbeam, D., Levin-Zamir, D., & Rowlands, G. (2018b). Health literacy and health
promotion in context. Global Health Promotion, 25(4), 3–5.
https://doi.org/10.1177/1757975918814436
Nutbeam, D., McGill, B., & Premkumar, P. (2018a). Improving health literacy in
community populations: a review of progress. Health Promotion
International, 33(5), 901–911. https://doi.org/10.1093/heapro/dax015
Okan, O., Lopes, E., Bollweg, T. M., Bröder, J., Messer, M., Bruland, D., Bond, E.,
Carvalho, G. S., Sørensen, K., Saboga-Nunes, L., Levin-Zamir, D., Sahrai, D.,
Bittlingmayer, U. H., Pelikan, J. M., Tomas, M., Bauer, U., & Pinheiro, P. (2018).
Generic health literacy measurement instruments for children and adolescents: a
systematic review of the literature. BMC Public Health, 18(1),
1–19. https://doi.org/10.1186/s12889-018-5054-0
Ospina, S. M., Esteve, M., & Lee, S. (2017). Assessing qualitative studies in public
administration Research. Public Administration Review, 78(4), 593–605.
https://doi.org/10.1111/puar.12837
O'Sullivan, E., Rassel, G., Berner, M., & Taliaferro, J. (2016). Research methods for
public administrators. Routledge.
Paakkari, L., & Okan, O. (2019). Health literacy—Talking the language of (school)
education. Health Literacy Research and Practice, 3(3), e161–e164.
https://doi.org/10.3928/24748307-20190502-01

155
Paakkari, L., Torppa, M., Mazur, J., Boberova, Z., Sudeck, G., Kalman, M., & Paakkari,
O. (2020). A comparative study on adolescents' health literacy in Europe: Findings
from the HBSC Study. International Journal of Environmental Research and
Public Health. (17)10, 3543. https://doi.org/10.3390/ijerph17103543
Palumbo, R. (2017). Examining the impacts of health literacy on healthcare costs. An
evidence synthesis. Health Services Management Research, 30(4), 197–212.
https://doi.org/10.1177/0951484817733366
Parker, R. M., & Ratzan, S. (2019). Re-enforce, not re-define health literacy—moving
forward with health literacy 2.0. Journal of Health Communication, 24(12),
923–925. https://doi.org/10.1080/10810730.2019.1691292
Pascale, R. T. (n.d.). Surfing the edge of chaos. Creative Management and
Development, 235-250. https://doi.org/10.4135/9781446213704.n18
Pelikan, J. M., Ganahl, K., & Roethlin, F. (2018). Health literacy as a determinant,
mediator and/or moderator of health: empirical models using the European health
literacy survey dataset. Global Health Promotion, 25(4), 57–66.
https://doi.org/10.1177/1757975918788300
Philippi, J., & Lauderdale, J. (2018). A Guide to field notes for qualitative research:
context and conversation. Qualitative Health Research, 28(3), 381–388.
https://doi.org/10.1177/1049732317697102
Pleasant, A., O’Leary, C., & Carmona, R. (2020). Health literacy: Global advances with a
focus upon the Shanghai declaration on promoting health in the 2030 agenda for
156
sustainable development. Information Services & Use, 40(1–2), 3–16.
https://doi.org/10.3233/ISU-200080
Prince, L. Y., Schmidtke, C., Beck, J. K., & Hadden, K. B. (2018). An assessment of
organizational health literacy practices at an academic health center. Quality
Management in Health Care, 27(2), 93–97.
https://doi.org/10.1097/QMH.0000000000000162
Rademakers, J., & Heijmans, M. (2018). Beyond reading and understanding: Health
literacy as the capacity to act. International Journal of Environmental Research and
Public Health, 15(8), 1676. https://doi.org/10.3390/ijerph15081676
Ratzan, S. C., & Parker, R. M. (2000). Health literacy. National library of medicine
current bibliographies in medicine: National Institutes of Health, US Department
of Health, and Human Services.
https://www.nlm.nih.gov/pubs/resources.html
Reinhart, R. M., Fink, A., Bhattarai, S., Cheng, J. J., Saha, A., Worten, K., Cronin, J., &
Shah, R. (2022). Engagement and bundle compliance during COVID-19: A virtual
strategy. Pediatric Quality & Safety, 7(2), e540.
https://doi.org/10.1097/pq9.0000000000000540
Rimer, B. K., & Glanz, K. (2005). Theory at a glance: A guide for health promotion
practice (2nd ed,). U.S. Department of Health and Human Services, National
Institutes of Health, National Cancer Institute.
Roberts, R. E. (2020). Qualitative interview questions: Guidance for novice researchers.
The Qualitative Report, 25(9), Article 1.
https://doi.org/10.46743/2160-3715/2020.4640

157
Roberts, T., Esponda, G. M., Krupchanka, D., Shidhaye, R., Patel, V., & Rathod, S.
(2018). Factors associated with health service utilization for common mental
disorders: a systematic review. BMC Psychiatry, 18(1), 1–19.
https://do.org/10.1186/s12888-018-1837-1
Rose, J., & Johnson, C. W. (2020). Contextualizing reliability and validity in qualitative
research: toward more rigorous and trustworthy qualitative social science in
leisure research. Journal of Leisure Research, 51(4), 432–451.
https://doi.org/10.1080/00222216.2020.1722042
Rosenhead, J., Franco, L. A., Grint, K., & Friedland, B. (2019). Complexity theory and
leadership practice: A review, a critique, and some recommendations. The
Leadership Quarterly, 30(5), Article e101304.
https://doi.org/10.1016/j.leaqua.2019.07.002
Rosenstock, I. M. (1966). “Why people use health services.” Milbank Memorial Fund
Quarterly 44, 94–127. https://doi.org/10.2307/3348967.
Rosenstock, I. M. (1974). Historical origins of the health belief model. Health Education
Monographs, 2(4), 328–335. https://doi.org/10.1177/109019817400200405
Rutberg, S., & Bouikidis, C. D. (2018). Focusing on the fundamentals: A simplistic
differentiation between qualitative and quantitative research. Nephrology Nursing
Journal, 45(2), 209–213. https://www.annanurse.org
Sadeghi, R., Hashemi, M., & Khanjani, N. (2018). The impact of educational intervention
based on the health belief model on observing standard precautions among emergency
center nurses in Sirjan, Iran. Health Education Research, 33(4),
158
327–335. https://doi.org/10.1093/her/cyy020
Saso, A., Skirrow, H., & Kampmann, B. (2020). Impact of COVID-19 on immunization
services for maternal and infant vaccines: Results of a survey conducted by
imprint—the immunizing pregnant women and infants’ network. Vaccines, 8(3),
556. https://doi.org/10.3390/vacines8030556
Saunders, M., Lewis, P., & Thornhill, A. (2019). Research methods for business students
(8th ed.). Pearson Education Limited.
Scherzinger, G., & Bobbert, M. (2017). Evaluation of research ethics committees:
Criteria for the ethical quality of the review process. Accountability in research,
24(3), 152-176. https://doi.org/10.1080/08989621.2016.1273778 Schillinger, D.
(2021). Social Determinants, Health Literacy, and Disparities:
Intersections and controversies. Health Literacy Research and Practice, 5(3).
234–243. https://doi.org/10.3928/24748307-20210712-01
Schneider, M., & Somers, M. (2006). Organizations as complex adaptive systems:
Implications of complexity theory for leadership research. The Leadership
Quarterly, 17(4), 351–365. https://doi.org/10.1016/j.leaqua.2006.04.006
Schwartzberg, J. G., Vangeest, J. B., & Wang, C. C. (Eds.). (2005). Understanding health
literacy: Implications for medicine and public health. American Medical Association,
69–84. https://doi.org/10.1111/j.1525-1497.2006.00547.x
Secretary’s Advisory Committee on National Health Promotion and Disease Prevention
objectives for 2030. (2019). History of health literacy definition. Healthy People

159
2030. https://health.gov/healthypeople/priority-areas/health-literacy-
healthypeople-2030/history-health-literacy-definitions
Sentell, T., Vamos, S., & Okan, O. (2020). Interdisciplinary perspectives on health
literacy research around the world: More important than ever in a time of
COVID-19. International Journal of Environmental Research and Public
Health, 17(9). 3010, https://doi:10.3390/ijerph17093010
Shao, S., Wang, M., Jin, G., Zhao, Y., Lu, X., & Du, J. (2018). Analysis of health service
utilization of migrants in Beijing using Andersen health service utilization model.
BMC health Services Research, 18(1), 1–11.
https://doi.org/10.1186/s12913-018-3271-y
Sharma, M. (2021). Theoretical foundations of health education and health promotion.
Jones & Bartlett Learning.
Sheppard, J., & Thomas, C. B. (2021). Community pharmacists and communication in
the time of COVID-19: Applying the health belief model. Research in Social and
Administrative Pharmacy, 17(1), 1984–1987.
https://doi.org/10.1016/j.sapharm.2020.03.017
Shrank, W. H., Rogstad, T. L., & Parekh, N. (2019). Waste in the U.S. healthcare
system: Estimated costs and potential for savings. Journal of American Medical
Association, 322(15), 1501–1509. https://doi.org/10.1001/jama.2019.13978
Simon, M. K. (2011). Dissertation and scholarly research: Recipes for success
(2011 Ed.). Dissertation Success, LLC. https://www.dissertationredicpes.com
Simonds, S. K. (1974). Health education as social policy. Health Education
160
Monographs, 2(1_suppl), 1–10. https://doi.org/10.1177/10901981740020S102
Simpson, R. M., Knowles, E., & O’Cathain, A. (2020). Health literacy levels of British
adults: A cross-sectional survey using two domains of the health literacy questionnaire.
BMC Public Health, 20, 1–13.
http://doi.org/10.1186/s12889-020-09727-w
Sisko, A. M., Keehan, S. P., Poisal, J. A., Cuckler, G. A., Smith, S. D., Madison, A. J.,
Rennie, K. E., & Hardesty, J. C. (2019). National health expenditure projections,
2018-2027 economic and demographic trends drive spending and enrollment
growth. Health Affairs, 38(3), 491–501. https://doi.org/10.1377/hlthaff.2018.05499
Skinner, C. S., Tiro, J., & Champion, V. L. (2015). Background on the health belief
model. Health behavior: Theory, Research, and Practice, 75–91.
SoleimanvandiAzar, N., Kamal, S. H. M., Sajjadi, H., Harouni, G. G., Karimi, S. E.,
Djalalinia, S., & Forouzan, A. S. (2020). Determinants of outpatient health service
utilization according to Andersen’s behavioral model: A systematic scoping review.
Iranian Journal of Medical Sciences, 45(6), 405–424.
https://doi.org/10.30476/ijms.2020.85028.1481
Sørensen, K., & Pleasant, A. (2017). Understanding the conceptual importance of the
differences among health literacy definitions. Studies in Health Technology and
Informatics, 240, 3–14. https://doi.org/10.3233/978-1-61499-790-0-3
Spoor, B., & Rothman, M. (2021). On the critical utility of complexity theory in
intelligence studies. Intelligence & National Security, 36(4), 555–568.
https://doi.org/10.1080/02684527.2021.1893076
161
Stenfors, T., Kajamaa, A., & Bennett, D. (2020). How to assess the quality of
qualitative research. The Clinical Teacher, 17(6), 596–599.
https://doi.org/10.111/tct.13242
Stielke, A., Dyakova, M., Ashton, K., & van Dam, T. (2019). The social and economic
benefit of health literacy interventions in the WHO EURO region. European
Journal of Public Health, 29(Supplement_4), 186–390.
https://doi.org/10.1093/eurpub.ckz186.390
Svendsen, M. T., Bak, C. K., Sørensen, K., Pelikan, J., Riddersholm, S. J., Skals, R. K.,
Mortensen, R. N., Maindal, H. T., Boggild, H., Nielsen, G., & Torp-Pedersen, C.
(2020). Associations of health literacy with socioeconomic position, health risk
behavior, and health status: a large national population-based survey among
Danish adults. BMC Public Health 20(1), 1–12.
https://doi.org/10.1186/s12889-020-08498-8
Theofanidis, D., & Fountouki, A. (2018). Limitations and delimitations in the research
process. Perioperative Nursing-Quarterly scientific, online official journal of
GORNA, 7(3), 155–163. https://doi.org/10.5281/zenodo.2552022
Trezona, A., Rowlands, G., & Nutbeam, D. (2018). Progress in implementing national
policies and strategies for health literacy—what have we learned so
far? International Journal of Environmental Research and Public Health, 15(7),
1–17. https://doi.org/10.3390/ijerph15071554
Turner, J. R., & Baker, R. M. (2019). Complexity Theory: An overview with potential
applications for the social sciences. Systems, 7(1), 4.
162
http://doi.org/10.3390/systems7010004
Tyrer, S., & Heyman, B. (2016). Sampling in epidemiological research: Issues, hazards,
and pitfalls. British Journal of Psychiatry Bulletin, 40, 57–60.
https://doi.org/10.1192/pb.bp.114.050203
Uemura, K., Yamada, M., & Okamoto, H. (2018). Effects of active learning on health
literacy and behavior in older adults: a randomized controlled trial. Journal of the
American Geriatrics Society, 66(9), 1721–1729.
https://doi.org/10.1111/jgs.15458
Vahedian-Shahroodi, M., Tehrani, H., Robat-Sarpooshi, D., GHolian–Aval, M., Jafari,
A., & Alizadeh-Siuki, H. (2021). The impact of health education on nutritional
behaviors in female students: An application of health belief model. International
Journal of Health Promotion and Education, 59(2), 70–82.
https://doi.org/10.1080/14635240.2019.1696219
Van Diepen, S., Tran, D. T., Ezekowitz, J. A., Zygun, D. A., Katz, J. N., Lopes, R. D.,
Newby, L. K., McAllister, F. A., & Kaul, P. (2018). The high cost of critical care unit
over-utilization for patients with NSTE acute coronary syndrome. American
Heart Journal, (202), 84–88. https://doi.org/10.1016/j.ahj.2018.05.003
Van Wyk, J., Bothma, T., & Holmner, M. (2020). "A conceptual virtual research
environment model for the management of research data, a South African perspective,"
Library Management, 4 (6/7), 417–446.
https://doi.org/10.1108/LM-02-2020-0037

163
Varpio, L., Ajjawi, R., Monrouxe, L. V., O’Brien, B. C., & Rees, C. E. (2017). Shedding
the cobra effect: Problematizing thematic emergence, triangulation, saturation, and
member checking. Medical Education, 51(1), 40–50.
https://doi.org/10.1111/medu.13124
Varpio, L., Young, M., Uijtdehaage, S., & Paradis, E. (2019). The distinctions between
theory, theoretical framework, and conceptual framework. Academic Medicine.
95(7), 989–994. https://doi.org/10.1097/acm.0000000000003075
Walters, R., Leslie, S. J., Polson, R., Cusack, T., & Gorely, T. (2020). Establishing the
efficacy of interventions to improve health literacy and health behaviors: A
systematic review. BMC Public Health, 20(1), 1–17.
https://doi.org/10.1186/s12889-020-08991-0
Williams, M., & Moser, T. (2019). The art of coding and thematic exploration in
qualitative research. International Management Review, 15(1), 45–55.
https://www.imrjournal.org
World Health Organization. (2017). Shanghai declaration on promoting health in the
2030 agenda for sustainable development. Health Promotion International, (3),
7–8. https://doi.org/10.1093/heapro/daw103
World Health Organization. (2020). Pulse survey on continuity of essential health
services during the COVID-19 Pandemic: Interim Report. 1–21
https://www.who.int/publications/i/item/WHO-2019-nCoV-EHS_continuitysurvey-
2020.1
164
Yeong, M. L., Ismail, R., Ismail, N. H., & Hamzah, M. I. (2018). Interview protocol
refinement: Fine-tuning qualitative research interview questions for multi-racial
populations in Malaysia. The Qualitative Report, (23)11, 2700–2713
https://doi.org/10.46743/2160-3715/2018.3412
Yin, R. K. (2018). Case study research and application: Design and methods (6th ed.).
Sage Publications.
Young, J. C., Rose, D. C., Mumby, H. S., Benitez‐Capistros, F., Derrick, C. J., Finch,
T., Garcia, C., Home, C., Marwaha, E., Morgans, C., Parkinson, S., Shah, J., Wilson,
K. A., & Mukherjee, N. (2018). A methodological guide to using and reporting on
interviews in conservation science research. Methods in Ecology and Evolution,
9(1), 10–19. https://doi.org/10.1111/204-210X.12828
Zheng, M., Jin, H., Shi, N., Duan, C., Wang, D., Yu, X., & Li, X. (2018). The relationship
between health literacy and quality of life: A systematic review and meta-analysis.
Health and Quality of Life Outcomes, 16(1), 1–10.
https://doi.org/10.1186/s12955-018-1031-7
Zheng, Z., Han, X., Zhao, J., Banegas, M. P., Tucker-Seeley, R., Rai, A., Fedewa, S. A.,
Song, W., Jemal, A., & Yabroff, K. R. (2020a). Financial hardship, healthcare
utilization, and health among US cancer survivors. American Journal of
Preventive Medicine, 59(1), 68–78.
https://doi.org/10.1016/j.amepre.2020.02.016

165
Zheng, Z., Jemal, A., Tucker-Seeley, R., Banegas, M. P., Han, X., Rai, A., Zhao, J., &
Yabroff, K. R. (2020b). Worry about daily financial needs and food insecurity
among cancer survivors in the United States. Journal of the National
Comprehensive Cancer Network, 18(3), 315–327.
https://doi.org/10.6004/jnccn.2019.7359

