



PHARMACOLOGY AND PARENTAL THERAPY DRUG
ADMINISTRATION REVIEW FOR NCLEX-RN
Legal aspects of medication administration
The
Joint
Commission
requires
that
two
patient
identifiers
(e.g.,
name,
birthday,
account
number)
be
checked prior to administration of any medication.
Components of a legal medication order
•Date and time
•Patient’s name
•Patient’s inpatient ID number
•Drug Name and strength of dose
•Frequency of dose
•Physician’s full signature
Nurse’s legal responsibility
•Interpret each component of the order
•Question the order by communicating with the physician if
The nurse cannot read the order
Any component of the order is erroneous or ambiguous
The nurse had any doubt about the appropriateness of the order
Any order which does to make sense, such as large number of tablets or
capsule. Or a large volume of solution for injection
Controlled Substances
⚫All controlled substances must be stored in a locked container requiring a key or
computerized access code for entry.
⚫An inventory record of all controlled substances used is maintained.
⚫If any part of a dose of a controlled substance is discarded, a second nurse witnesses the
disposal and the record is signed by both nurses. (Agency policies and procedures are always
followed.)
⚫Agency policies and procedures are followed with regard to the counting of controlled
substances at the end of a shift; any discrepancy in the count is reported immediately.
Before Administration
⚫Wash your hands.
⚫Assess the prescription and compare new medication prescriptions with the current list of
medications (reconciliation).

⚫Ask the client whether he or she has a history of allergies.
⚫Determine the purpose of the medication.
⚫Assess the client for existing medical disorders in which the prescribed medication is
contraindicated (e.g., many medications are contraindicated in pregnancy and for breastfeeding
clients).
⚫Check the client’s age (the older client and the neonate are at greater risk for toxicity than is an
adult client).
⚫Assess the client’s vital signs and significant laboratory results (e.g., the potassium level in a
client who has been prescribed a loop diuretic).
⚫Assess the client’s understanding of the purpose of the prescribed medication.
⚫Identify and address concerns (e.g., social, cultural, religious) that the client has with regard to
taking the medication.
⚫Use the appropriate resources (e.g., medication formulary, pharmacist) as necessary when
preparing the medication.
During Administration
⚫Assess the six rights: right medication, right dose, right client, right route, right time, and right
documentation.
⚫Assess the need for conversion or calculation of a dose when preparing medication for
administration.
⚫Administer the medication within 30 minutes of the prescribed time.
⚫Avoid administering medications with antacids, which affect absorption of medication. Also
avoid administering medications with grapefruit juice, which contains an enzyme that inhibits
absorption of many medications.
After Administration

⚫Do not recap needles; discard needles in an appropriate container, using the safety device
provided with the syringe if one is available.
⚫Dispose of any unused medication in accordance with agency policy: Liquid medication may be
discarded in a sink or flushed down a toilet; tablets or capsules may be flushed down the toilet.
Never discard medication in a trash container.
⚫Document administration of the medication given at€” including its name, the dose, the date
and time, and your initials at€” immediately after giving the medication.
⚫Monitor the client for side effects or adverse effects (e.g., allergic reaction) to the medication
and take action if adverse effects occur.
⚫Evaluate the client for a therapeutic response to the medication.
Administering Oral Medications
⚫Pour tablets or capsules into the medication container's cap, not your hand. Medications
prepared for unit dosage may be opened at the time of administration in the client's room.
⚫Scored tablets (those marked to facilitate division) may be divided into halves or quarters.
⚫Enteric-coated tablets and sustained-released capsules must not be crushed.
⚫To pour medication accurately using a medicine cup, hold the cup at eye level, then pour to the
line designating the desired measure of medication.
⚫Volumes of less than 5 mL are measured with the use of a syringe from which the needle has
been removed.
⚫A calibrated dropper is used to give medicine to a child or to add a small amount of liquid to
water or juice.
⚫Do not mix liquids with tablets or liquids with liquids in the same container.
Sublingual Buccal (under the tongue) and (between the cheek and the gum):
⚫Instruct clients to keep the medication in place until it is absorbed.
⚫Clients should not eat or drink while the tablet is in place.
Liquids, Suspensions, & Elixirs:
⚫Follow directions for dilution and shaking.
⚫When administering the medication, the base of the meniscus (lowest fluid line) is at the level of
the desired dose.
Standard precautions require the wearing of gloves when placing a tablet under a patient’s tongue.
The patient should not chew a sublingual tablet and should not drink or swallow until the tablet is
completely dissolved and absorbed.
Nasogastric and Gastrostomy Tubes
Check for proper tube placement.
Use a syringe and allow the medication to flow in by gravity, or push in with the plunger of the
syringe.
General guidelines
⚫Use liquid forms of medications.
⚫Do not give sublingual medications.
⚫Do not crush specially prepared oral medications (extended/time-release, fluid-filled, enteric
coated).
⚫Check the compatibility of medications before mixing.
⚫Do not mix medications with enteral feedings.
⚫To prevent clogging, flush the tubing before and after each medication with 5 to 30 mL of warm
water.
⚫When administration of medications is complete, flush with 30 to 60 mL of warm water.
Keeping the drugs separate allows for accurate identification if a dose is spilled.
The patient should be positioned in a semi-Fowler’s or Fowler’s position during and after
administration of medications via a nasogastric tube to reduce the risk of aspiration.
Parenteral Medications
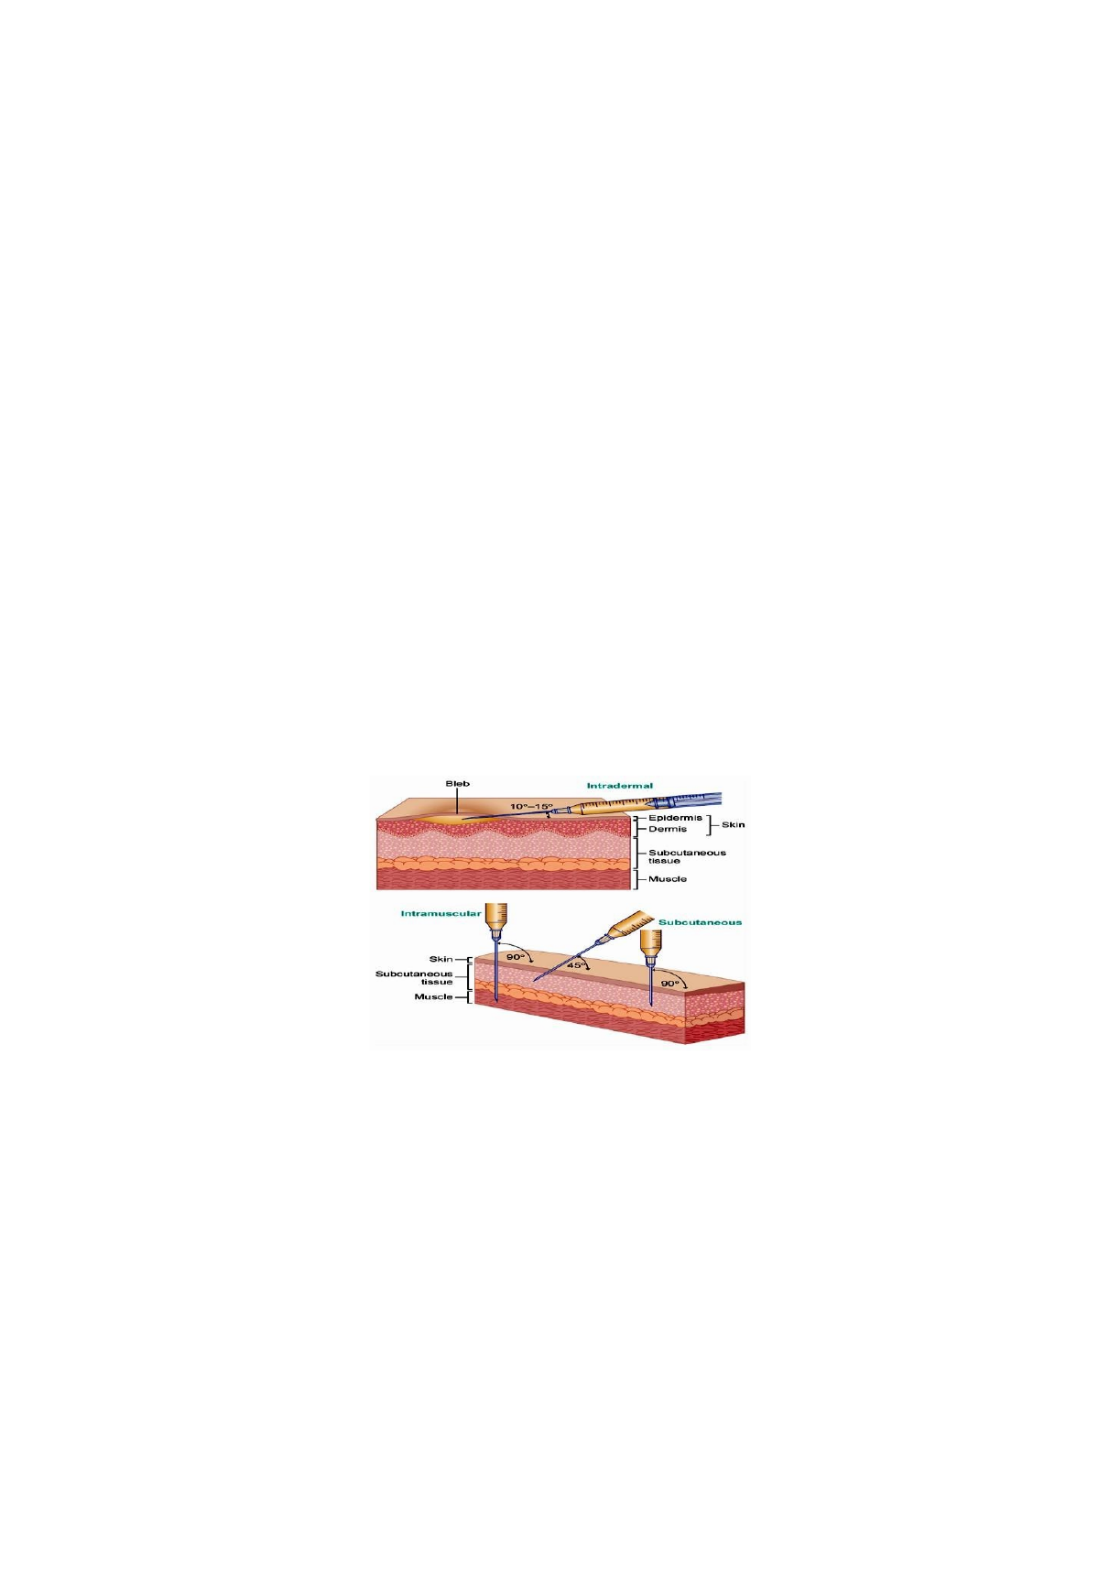
⚫Parenteral medications are administered by way of subcutaneous, intramuscular, or intradermal
injection or the intravenous route.
⚫These medications are packaged in ampules, vials, and premeasured syringes and cartridges.
General Considerations:
⚫The vastus lateralis site is usually the recommended site for infants and children < 2 years of
age.
⚫After age 2, the ventral gluteal site can be used. Both of these sites can accommodate fluid up to
2 mL. The deltoid site has a smaller muscle mass and only can accommodate up to 1 mL of fluid.
⚫Use a needle size and length appropriate to the type of injection and client size. Syringe size
should approximate the volume of medication.
⚫Use a tuberculin syringe for solution volume < 0.5 mL.
⚫Rotate injection sites to enhance medication absorption, and document each site used.
⚫Do not use injection sites that are edematous, inflamed, or have moles, birthmarks, or scars.
⚫If medication is given intravenously, immediately monitor the client for therapeutic and
side/adverse effects.
⚫Discard all sharps (broken ampule bottles, needle) in designated containers. Containers should
be leak- and puncture-proof.
Intradermal:
⚫This route is usually used for tuberculin testing or checking for medication/allergy sensitivities.
⚫It may be used for some cancer immunotherapy.
⚫Use small amounts of solution (0.01 to 0.1 mL) in a tuberculin syringe with a fine-gauge needle
(26 to 27)
⚫In lightly pigmented, thin-skinned, hairless sites (inner surface of midforearm or scapular area of
back) at a 10 to 15o angle.
Tuberculin Syringe
The tuberculin syringe, holding 1 mL, is used to measure small or critical amounts of medication (e.g., an
allergen extract or vaccine or a child's medication).
⚫It may also be used to inject medication intradermally for diagnostic testing (e.g., tuberculin
testing).
⚫This syringe is calibrated in hundredths (0.01) of a milliliter.
In general, 3 to 4 finger widths below the antecubital space and 1 hand width above the wrist is the
preferred location on the forearm.
Subcutaneous:
⚫This route is appropriate for small doses of nonirritating, water-soluble medications and is
commonly used for insulin and heparin.
⚫Use a 3/8- to 5/8-inch, 25- to 27-gauge needle, or an insulin syringe of 28- to 31-gauge.
⚫Inject no more than 1.5 mL solution.
⚫For an average-size client, pinch up skin and inject at a 45 to 90o angle. For an obese client, use
a 90o angle.
⚫Sites are selected for adequate fat-pad size (abdomen, upper hips, lateral upper arms, thighs).

Insulin Syringe
The standard U-100 insulin syringe is used to measure U-100 insulin only; it is calibrated for a total of
100 units, or 1 mL.
⚫Insulin should not be measured in any other type of syringe.
⚫When a prescription indicates that regular and NPH insulin are to be combined, remember :RN
Draw up the insulin first, then the regular NPH insulin.
The proper technique for subcutaneous injections involves the use of a 1/2- to 5/8-inch needle, 25-
gauge, at a 45- or 90-degree angle of insertion dependent on patient size, and aspiration is not done
with anticoagulants and insulin. The landmark for the vastus lateralis is one handbreadth below the
greater trochanter and above the knee on the outer aspect of the thigh.
Intramuscular:
⚫This route is appropriate for irritating medications, solutions in oils, and aqueous suspensions.
⚫Most common sites include ventrogluteal, dorsogluteal,
⚫deltoid, and vastus lateralis (pediatric).
⚫Use needle size 18 to 27 (usually 22- to 25-gauge), 1 to 1 1/2 inches long, and inject at a 90o
angle.
⚫Volume injected is usually 1 to 3 mL. If a greater amount is required, divide into two syringes
and use two sites.
Z-Track Technique:
⚫Z-track is a type of IM injection that prevents medication from leaking back into subcutaneous
tissue.
⚫It is often used for medications that cause visible and/or permanent skin stains such as certain
iron preparations.
⚫The Z-track method prevents medication from leaking into subcutaneous tissues where it can be
irritating and/or painful. This method should be used with medications that are particularly
irritating to the tissue. Some institutional policies require the use of the Z-track method with all
intramuscular injections.
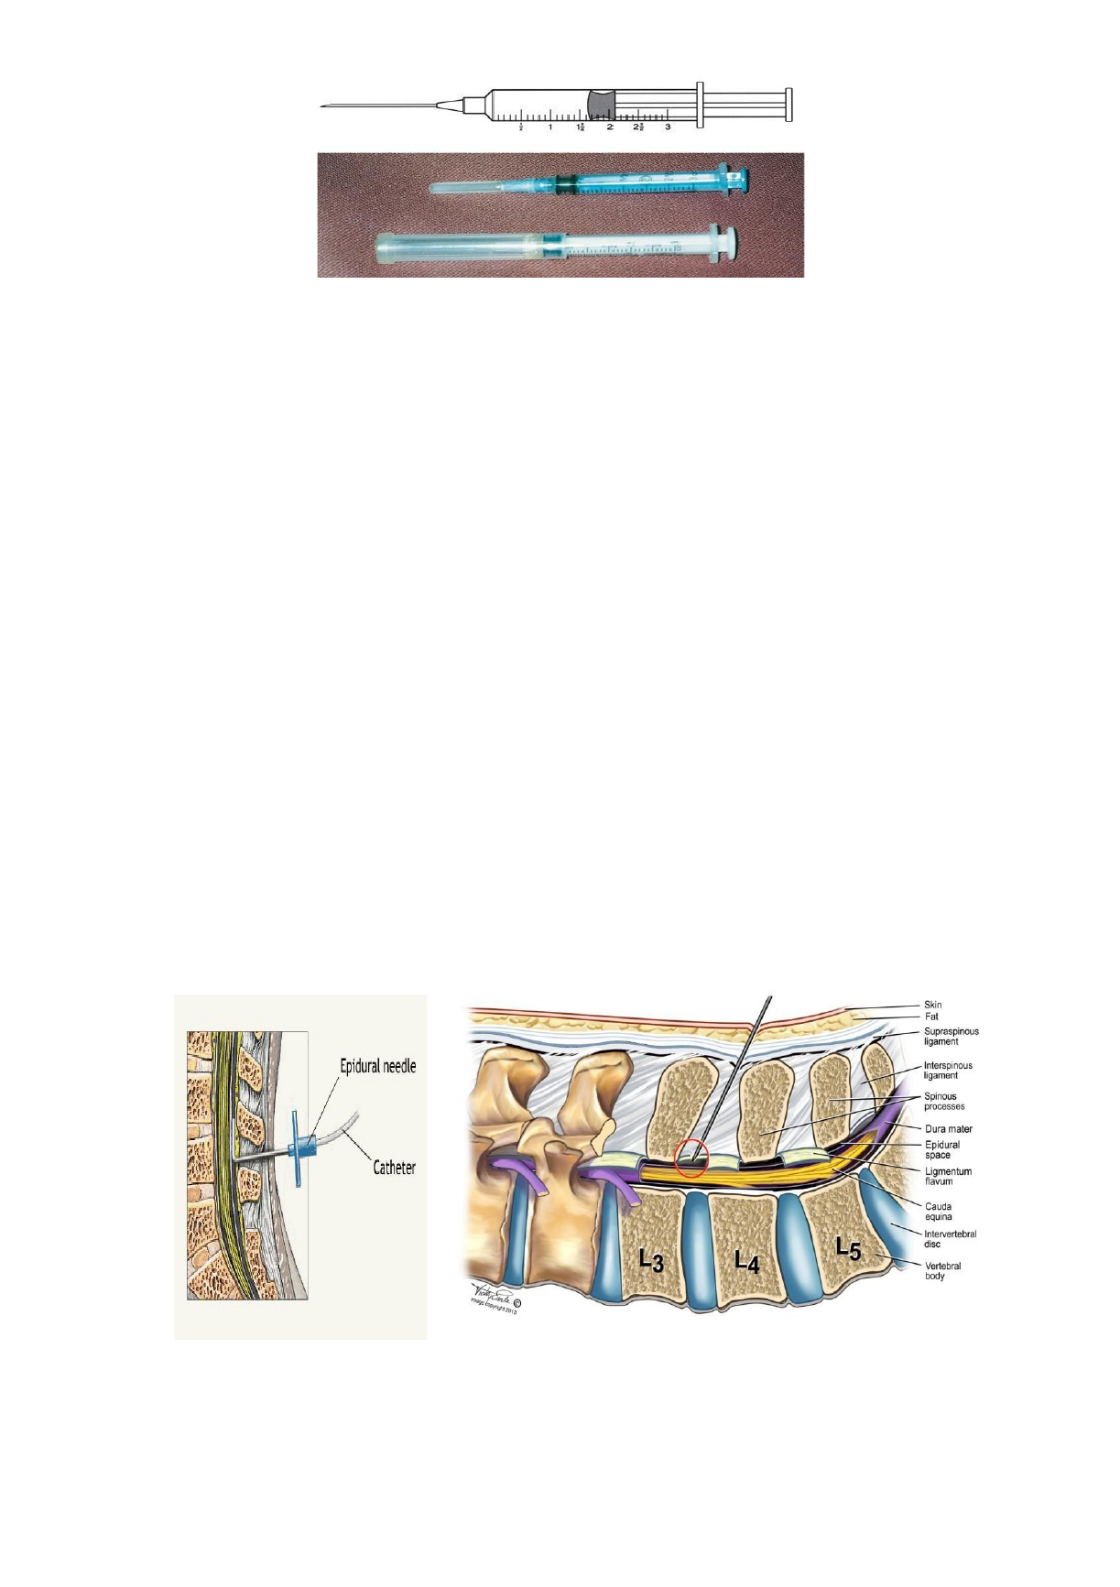
The standard 3-mL syringe:
This is calibrated in tenths of a milliliter.Standard medication doses for adults are to be rounded to
the nearest tenth (0.1) of a milliliter.
⚫The nurse should not administer more than 3 mL per intramuscular or subcutaneous injection
site; when a volume greater than 3 mL is required, a 5-mL syringe, calibrated in fifths, may be
used.
The dorsogluteal injection site is no longer recommended for injections because of the close proximity
to the sciatic nerve and major blood vessels. Injury to the sciatic nerve from an injection may cause
partial paralysis of the leg. The dorsogluteal site is not to be used for intramuscular injections.
0.2 mL of air should be withdrawn into the syringe to provide an airlock and prevent the leakage of
medication back into the subcutaneous tissue.
Intravenous:
⚫This route is appropriate for administration of medications, fluid, and blood products.
⚫Vascular access devices can be for short-term use (catheters) or long-term use (infusion ports).
⚫Use 16-gauge for trauma clients, 18-gauge for surgical clients, and 22- to 24-gauge for children,
older adults, medical clients, and stable postoperative clients.
⚫Preferred sites are peripheral veins in the arm or hand.
⚫Ask the client which site he or she prefers.
⚫In neonates, veins of the head, lower legs, and feet may be used.
⚫After administration, immediately monitor for therapeutic and side/adverse effects.
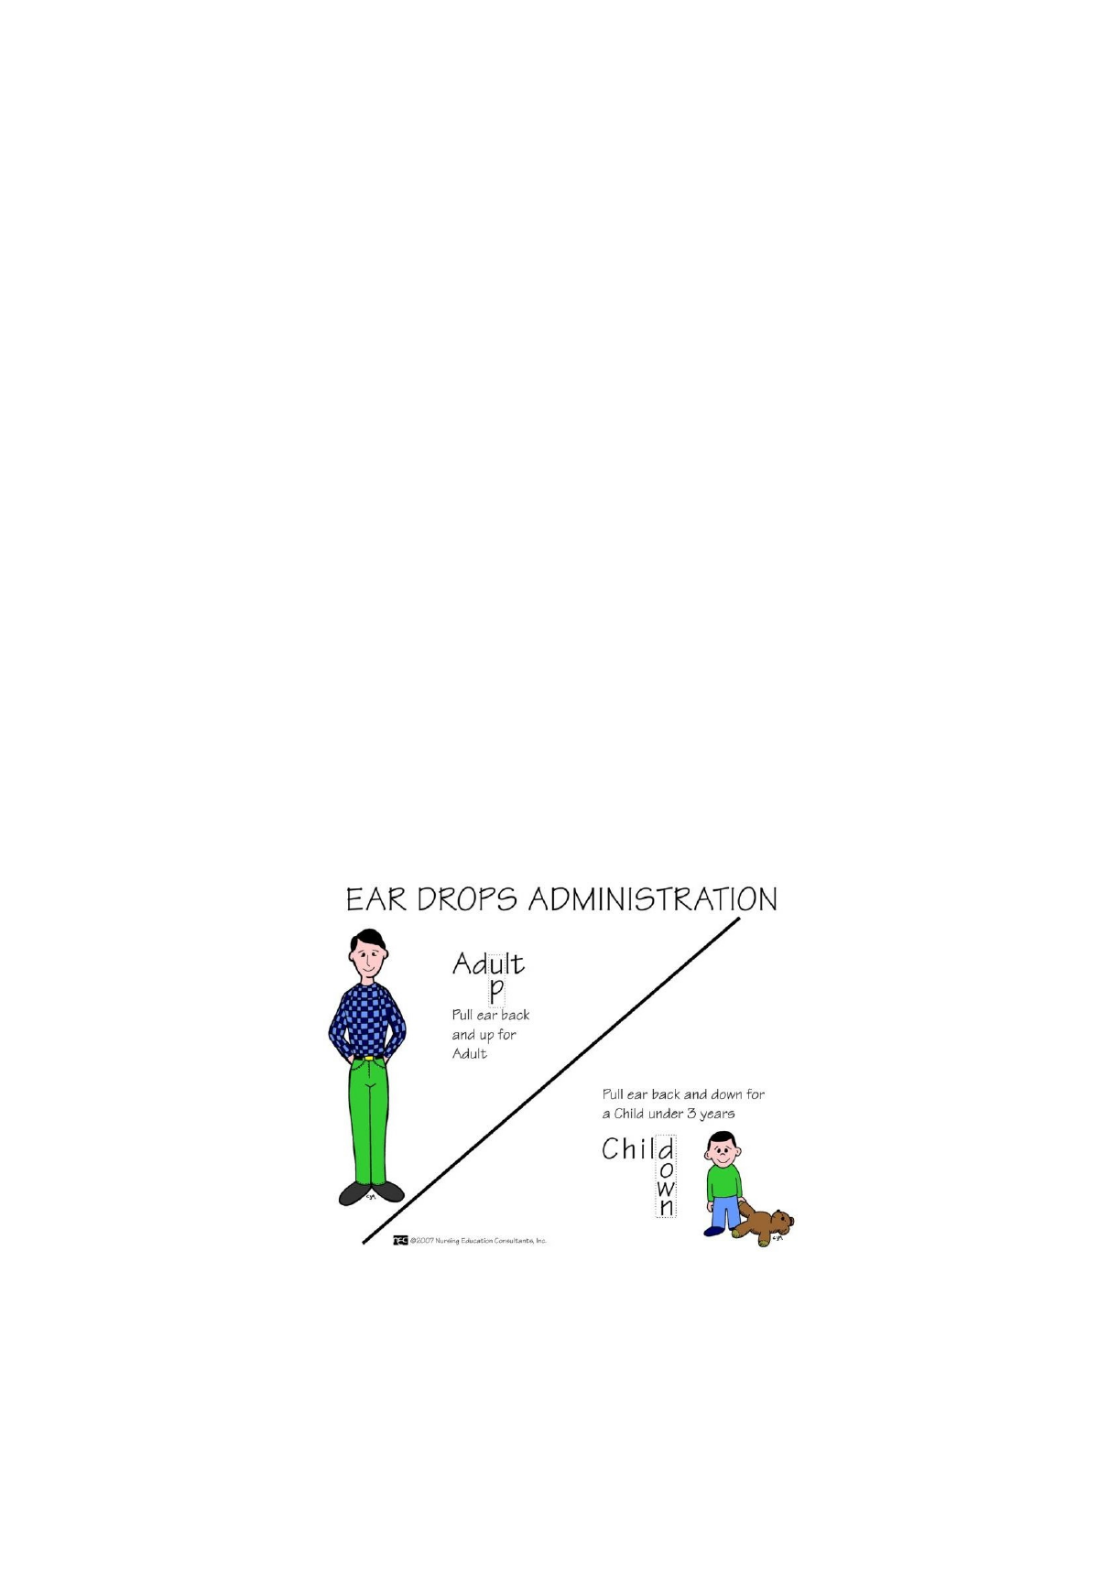
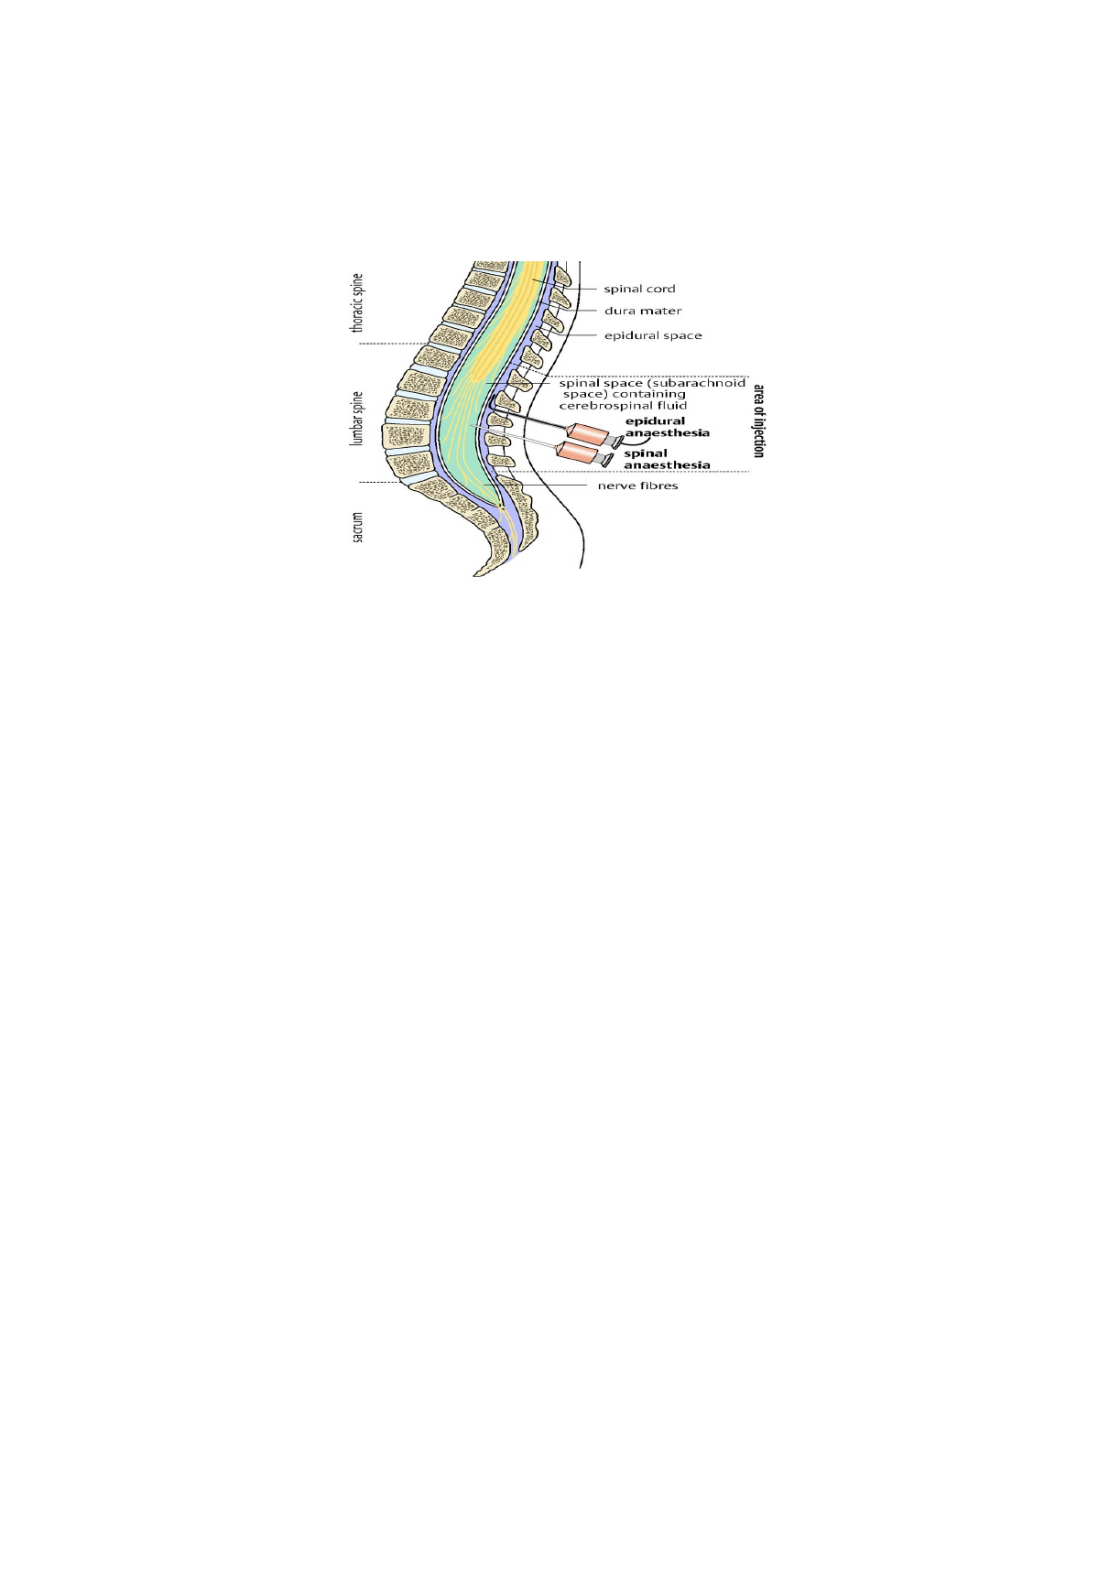
Epidural:
⚫Administration of intravenous opioid analgesia (morphine [Duramorph] or fentanyl [Sublimaze]).
⚫A catheter is advanced through a needle that is inserted into the epidural space at the level of
the fourth or fifth vertebrae.
⚫Infusion pumps are necessary to administer medication.
Injectable Medications in Powder Form
⚫Some medications become unstable when stored in solution and are therefore packaged in
powder form.
⚫Powders must be dissolved with sterile diluent, or reconstituted, before use; usually sterile
water or normal saline solution is used.
⚫Certain steps must be followed when a medication is reconstituted:
1. First locate the instructions on the label or in the vial's package insert. Read and follow the
directions carefully.
2. The instructions will state the volume and type of diluent to be used and the resulting volume of
the reconstituted medication.
3. Often the powdered medication adds volume to the solution in addition to the amount of
diluent that is required.
4. When reconstituting a multiple-dose vial, label the vial with the date and time of preparation,
your initials, and the date of expiration. It is also important to label the strength per volume.
Eye drops, Ointments, & Eardrops
⚫Drops: Place medication in the lower conjunctival sac and instruct the client to blink one or two
times, then keep the eyes closed for several minutes.
⚫Ointment: Squeeze a strip about a quarter-inch long (unless otherwise indicated) into the lower
conjunctival sac and instruct the client to gently close his or her eyes and keep them closed for 2
to 3 minutes.
⚫Eardrops: Instruct the client to lie on the unaffected side or to tilt the head toward the
unaffected side and to remain in this position for 2 minutes after administration.
⚫Next, pull back the pinna: In an adult client or older child, pull the pinna up and back; in an
infant or child younger than 3 years, pull the pinna down and back.

The eyedropper is held 1 to 2 cm above the conjunctival sac. The nurse should drop the prescribed
number of drops into the conjunctival sac. Never apply eye drops to the cornea. If the drops land on
the outer lid margins (e.g., if the patient moved or blinked), the procedure should be repeated.
Antianginal Transdermal Patch or Ointment
⚫Remove the old patch or ointment and cleanse the skin.
⚫Avoid touching the inside of the patch or the ointment (wear gloves).
⚫Avoid applying the patch or ointment to skin with hair.
⚫When using ointment, measure out the correct amount on the appropriate paper applicator and
tape the paper in place on the skin.
⚫Do not rub the ointment into the client's skin.
Respiratory Inhaler
1. Shake inhaler well and remove the mouthpiece cover.
2. Breathe out through the mouth, expelling air.
3. Place the lips securely around the mouthpiece and inhale, pushing the top of the medication
inhaler once while inhaling.
4. Hold the breath for a few seconds, then exhale slowly.
5. If a second inhalation is prescribed, wait 1 to 2 minutes before administering it.
6. A spacer may be used to keep the medication in the device longer thereby increasing the
amount of medication delivered to the lungs and decreasing the amount of the medication in
the oropharynx.
Rectal Suppository:
⚫To administer a suppository rectally, place the client in the Sims position.
⚫Lubricate the suppository and insert it, pointed end first, through the anal sphincter at€” about
4 inches in an adult, 2 inches in a child.
⚫Instruct the client to remain supine for 5 to 10 minutes.
Vaginal Suppository:
⚫To administer a suppository vaginally, first place the client in the lithotomy position.
⚫Lubricate the suppository and insert it 2 to 3 inches, toward the sacrum.
⚫Instruct the client to remain in the supine position for 5 to 10 minutes (offer a perineal pad).
INTRAVENOUS THERAPY
General Guidelines
⚫Check the prescription; if the nurse has questions, he or she must contact the physician to verify
the accuracy of the prescription.
⚫Determine the purpose of the solution (e.g., to remedy dehydration).
⚫Determine the client’s understanding of the purpose of the IV infusion.
⚫Identify and address concerns (e.g., social, cultural, religious) that the client may have about IV
therapy.
⚫Ask the client whether he or she has a history of allergies (e.g., latex).
⚫Caution is required in the administration of IV fluids to certain clients.
⚫Assess vital signs and the pertinent laboratory results.
⚫Document the IV solution (the name of the solution, the date and time when the infusion was
initiated, the flow rate, the site and appearance of the infusion, and your initials) immediately
after initiation of the infusion and after assessment.
⚫Monitor the client for adverse effects of the therapy (e.g., infiltration, phlebitis).
⚫Evaluate the client for a therapeutic response to the treatment.
Commonly Used IV Solutions
⚫Isotonic Solutions: Concentration of solute is similar to plasma. The osmotic pressure is
constant inside and outside the cells, therefore, fluid in each compartment remains, no shift
occurs. Cells neither shrink nor swell because fluid is distributed between intravascular and
interstitial (extracellular).
⚫Hypotonic Solutions: Lower concentration of solutes than plasma. It causes fluid to shift from
intravascular space to intracellular and interstitial spaces. Cells swell, but may deplete
intravascular fluid (plasma, circulatory system).
⚫Hypertonic Solutions: Rarely used. Higher concentration of solute than plasma. It causes fluid to
shift from intracellular space to extracellular (intravascular and interstitial) spaces. Used as
volume expanders, hyponatremia, and cerebral edema.
Solution Type Uses
0.9% NaCl
(Sodium Chloride)
(Normal Saline)
(NS)
Isotonic
Composition:
Water
Na: 154 mEq/l
Cl: 154 mEq/L
Use to increase fluid volume in extracellular
spaces. Examples are: Hemorrhage, sever e
vomiting or diarrhea, heavy drainage from GI
suction, fistulas or wounds.
Also mild hyponatremia, hypercalcemia, and
metabolic acidosis. Fluid of choice for
resuscitation efforts (patient in shock).

Lactated Ringer’s
(LR)
(Hartmann Solution)
Isotonic
Composition:
Na:130 mEq/l
K: 4 mEq/l
Ca: 3 mEq/l
Cl: 103 mEq/l
Its electrolyte content is most closely related to
blood serum and plasma. Therefore, it is more
beneficial for patients who require electrolyte
replace.
Alkalinizing Solution: The lactate is metabolized
into bicarbonate by the liver, so LR is often used
to correct metabolic acidosis.
Another choice for resuscitation efforts,
especially for fluid loss in burns and trauma. Also
for patient with acute blood loss (hypovolemia)
0.9% NaCl
(Sodium Chloride)
(Normal Saline)
(NS)
Isotonic Use to increase fluid volume in extracellular spaces.
Examples are: Hemorrhage, sever e vomiting or
diarrhea, heavy drainage from GI suction, fistulas
or wounds. Also mild hyponatremia,
hypercalcemia, and metabolic acidosis. Fluid of
choice for resuscitation efforts (patient in shock).
Lactated Ringer’s
(LR)
(Hartmann Solution)
Isotonic Used to remedy extracellular fluid deficits (e.g., fluid
loss from burns, bleeding, or dehydration
resulting from loss of bile or diarrhea).
5% dextrose in water
(D5W): isotonic
Replaces deficits of total body water.
Not generally used alone to expand extracellular
fluid volume because dilution of electrolytes may
occur.
5% dextrose in 0.225%
saline (5% D and 1/4 NS):
isotonic
5% dextrose in 0.45%
saline (5% D and 1/2 NS):
hypertonic
Used as initial fluid for hydration because it provides
more water than sodium.
Commonly used as maintenance fluid.
Inserting an IV Catheter
⚫Prepare the client for the insertion procedure (i.e., the procedure and what to expect in terms
of discomfort).
⚫Use sterile technique when inserting the IV and whenever working with an IV.
⚫Determine the client's dominant side and select the opposite side for venipuncture.
⚫Once a side has been selected, carefully choose a site.
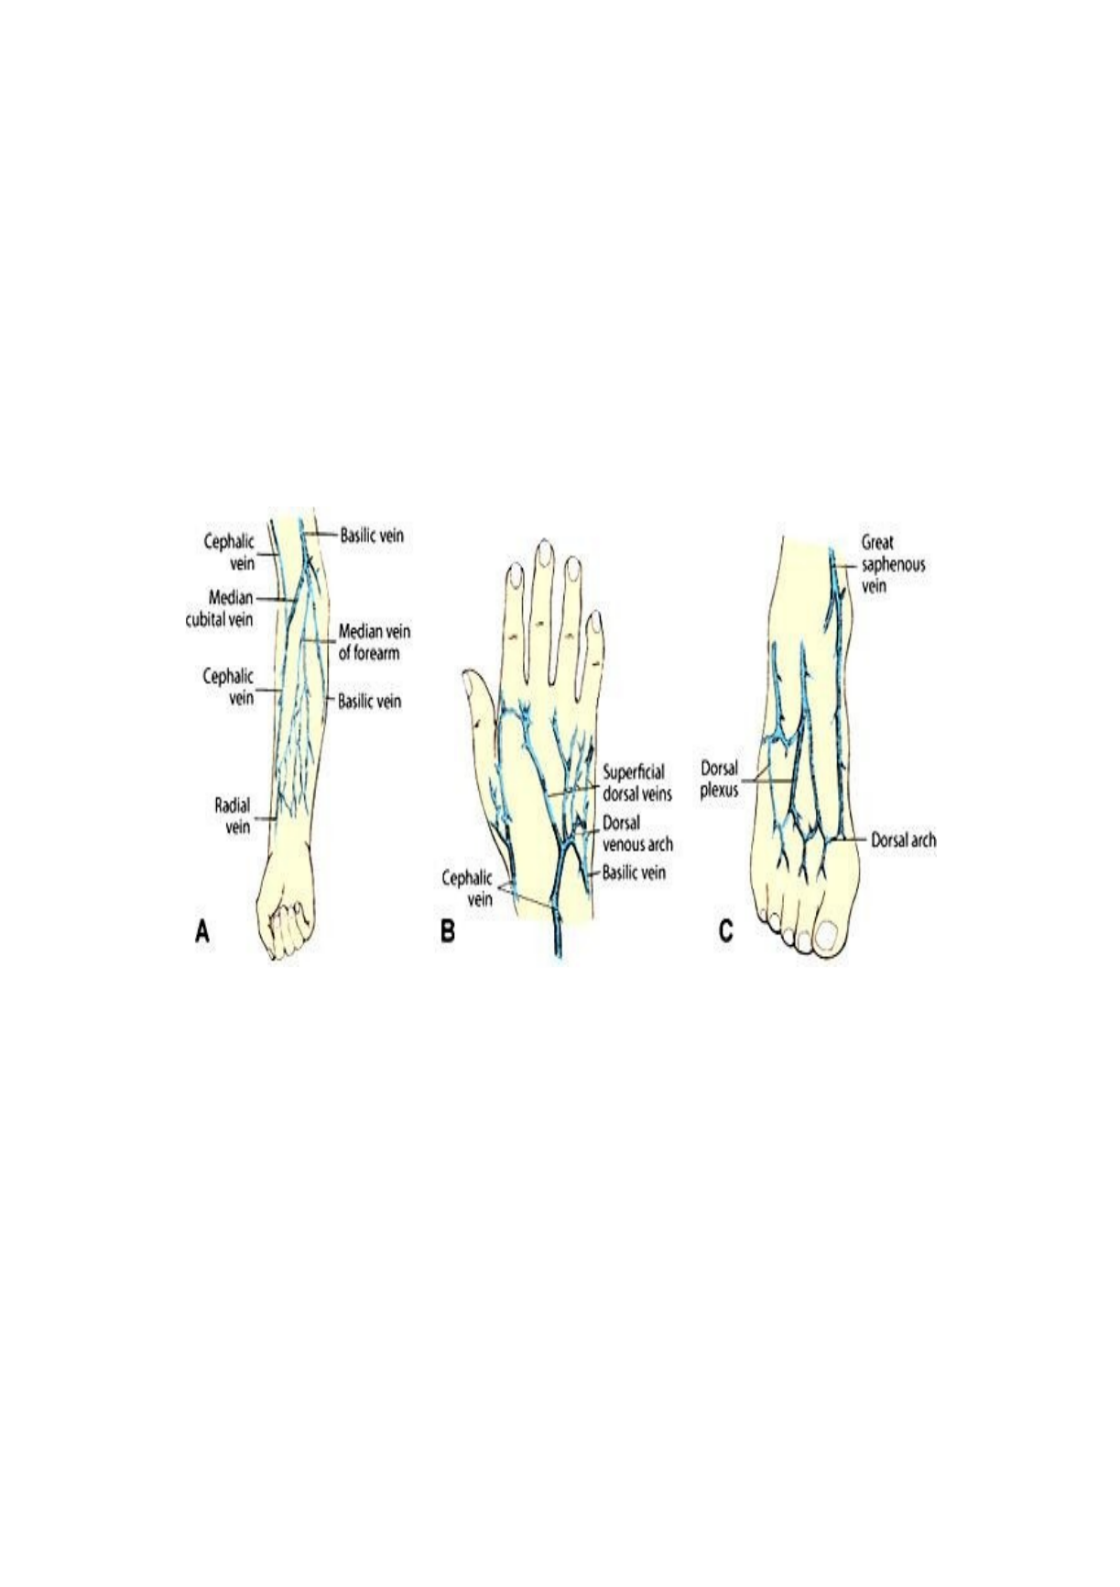
⚫When inserting the IV, clean the skin with an antimicrobial solution (per agency procedure),
using an inner to outer circular motion.
⚫Prime the tubing to remove air from the system.
⚫Start the IV infusion distally to provide the option of proceeding up the extremity to
other access areas if the vein is ruptured or if infiltration occurs; if infiltration occurs from
the antecubital vein, the lower veins generally cannot be used for puncture sites.
⚫Bending the elbow of the arm with an IV may obstruct the flow of solution, causing infiltration
that could lead to thrombophlebitis; use an arm board when the venipuncture site is located in
an area of flexion.
⚫Do not place restraints over the venipuncture site.
⚫Label the tubing, dressing, and solution bags clearly, indicating the date and time of the
initiation of the infusion; document the procedure and the client’€™s tolerance of it.
Maintaining IV Access
⚫Maintain aseptic technique.
⚫Check an adult’s IV flow rate and infusion site every 30 minutes; check a child’s every 15
minutes.
⚫Avoid checking the blood pressure on the arm with the IV.
⚫Change the venipuncture site every 72 hours or as specified by agency policy.
⚫Change the IV dressing every 72 hours, when the dressing is wet or contaminated, and as
otherwise specified by agency policy.
⚫Change the IV tubing every 72 hours or as specified by agency policy. (Central line tubing is
changed every 24 hours.)
⚫As a means of helping prevent sepsis, do not let an IV bag or bottle hang for more than 24
hours.
⚫To help prevent bacterial contamination, do not allow IV tubing to touch the floor.
Removing an IV Catheter
⚫Check the physician’s prescription, explain the procedure to the client, and ask the client to hold
the extremity still during cannula/needle removal.
⚫Turn the IV tubing clamp off and remove the dressing and tape covering the site while stabilizing
the catheter.
⚫Apply light pressure with sterile gauze or other material as specified by agency procedures over
the site and withdraw the catheter in a slow, steady movement, keeping the hub parallel to the
skin.
⚫Apply pressure for 2 to 3 minutes, using dry sterile gauze (apply pressure for a longer period
if the client has a bleeding disorder or is taking anticoagulant medication).
⚫Inspect the site for redness, drainage, and swelling and check the catheter for intactness.
⚫Document the procedure and the client’s response.
IV Gauges
⚫The lower the gauge number, the larger the outside diameter of the cannula.
⚫The gauge is chosen on the basis of the solution to be administered and the diameter of the
available vein.
⚫Larger gauges allow a higher flow rate than do smaller ones and permit the administration
of higher concentrations of solution.
⚫For the administration of blood products and anesthetics and the rapid administration of
emergency fluids, a large gauge is used (e.g., 14, 16, 18, or 19).
⚫For lipids (fat emulsion) infusions, a gauge of 20 or 21 is used.
⚫For standard IV fluids and clear-liquid IV medications, a gauge of 22 or 24 is used.
⚫If the client has very small veins, a gauge of 24 or 25 is used.
⚫In an older client, a small-gauge IV catheter, preferably 21 gauge or smaller, is used.
Intravenous Devices
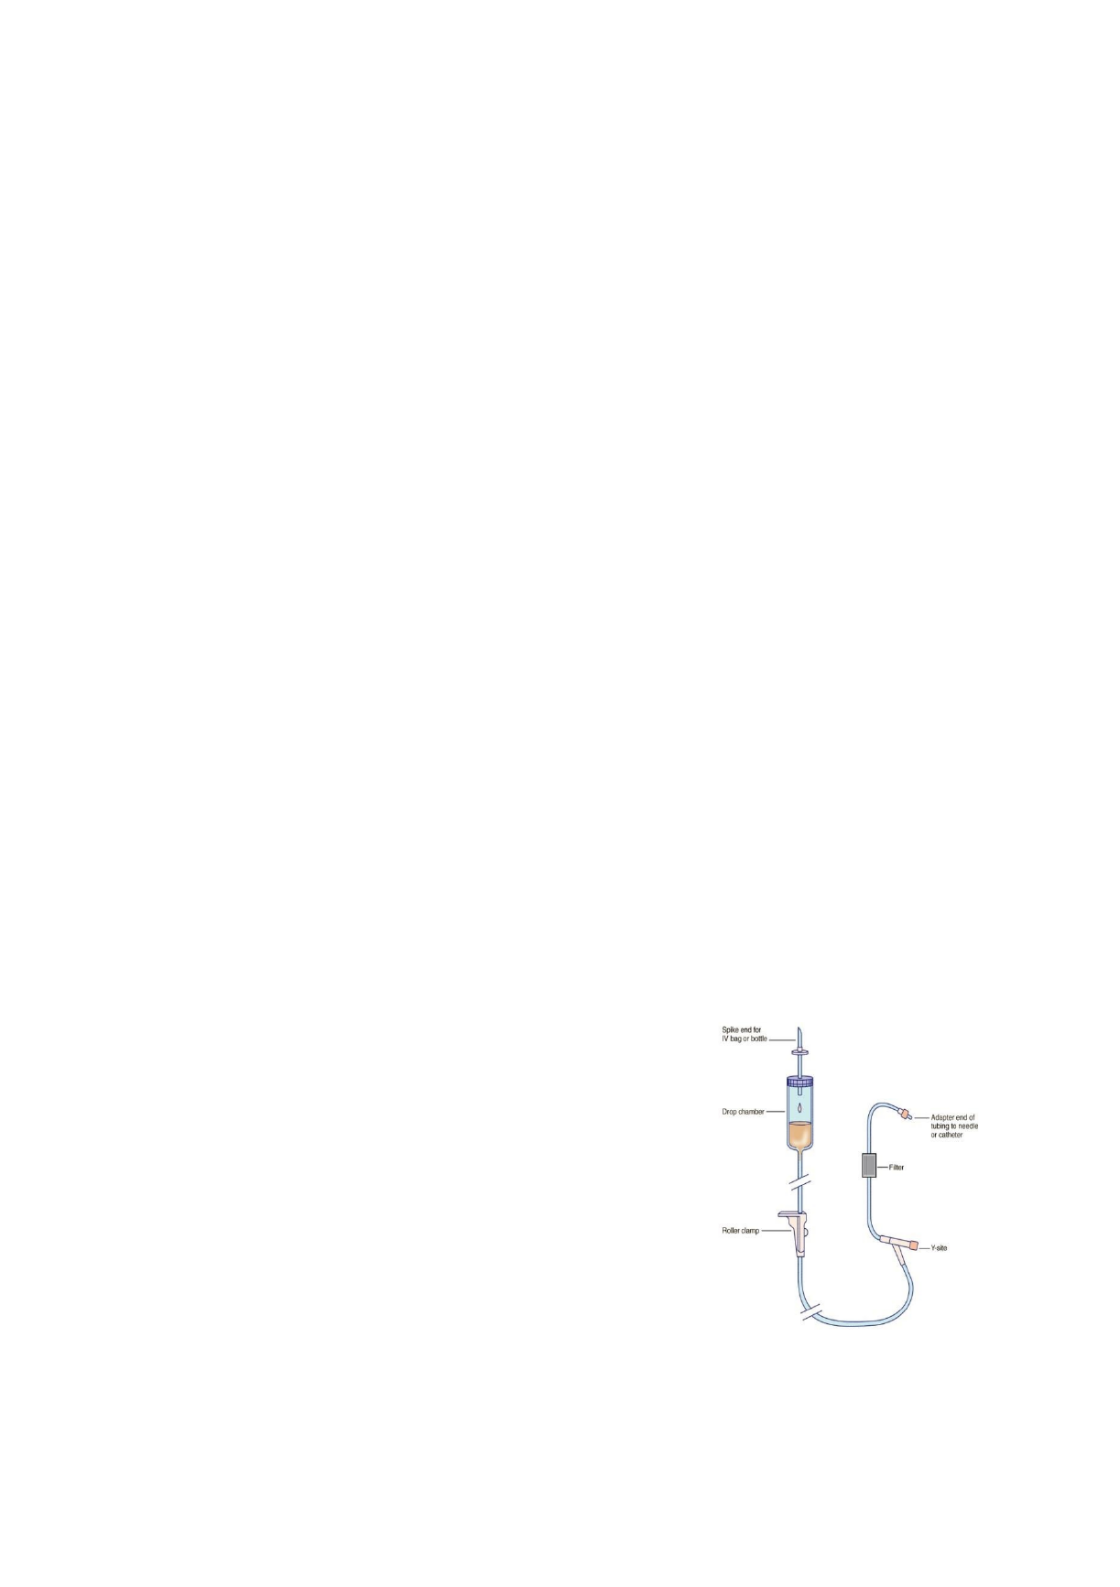
IV Tubing
Add extension tubing for children, clients who are restless, and clients
with special mobility needs.
⚫Use shorter secondary tubing for piggyback solutions,
connecting them to the injection sites nearest the drip chamber.
⚫Use special tubing for medication that is absorbed by plastic.
⚫
Vented and Nonvented Tubing
⚫A vent allows air to enter the IV container as the fluid leaves.
⚫Use vented tubing for glass or rigid plastic containers to allow
air to enter and displace the fluid as it leaves; fluid will not flow
from a rigid IV container unless it is vented.
⚫Use nonvented tubing for flexible containers.
Drip Chambers
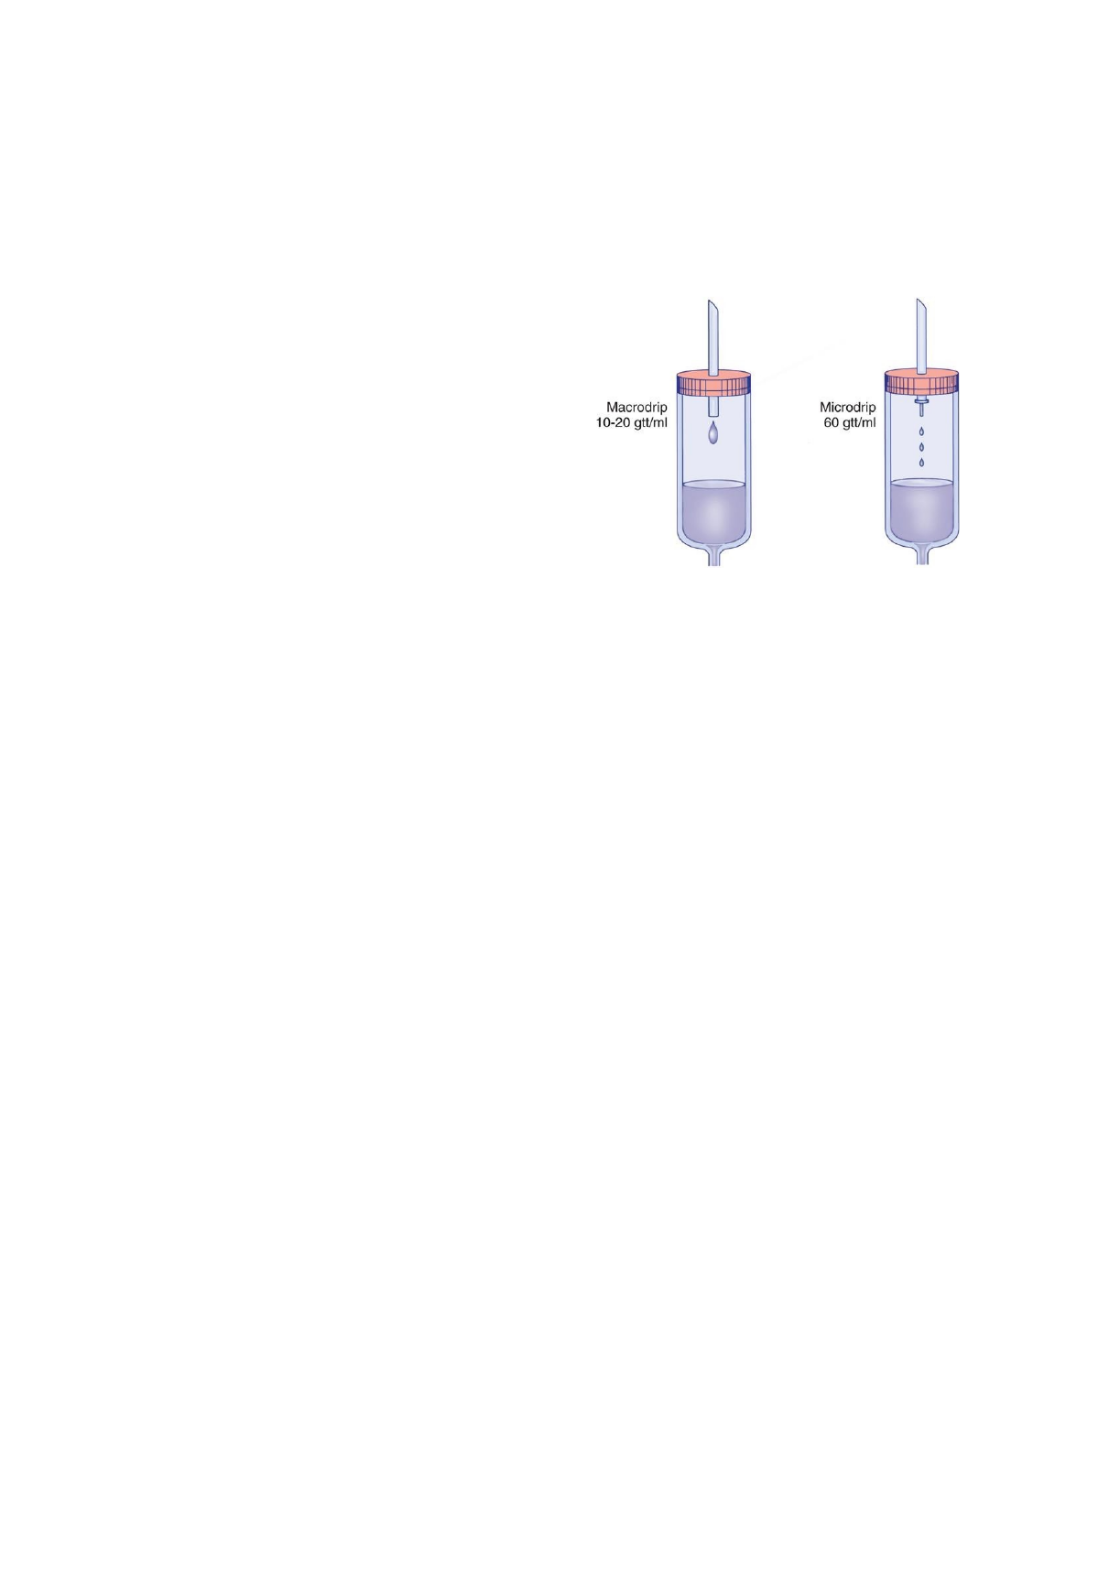
Microdrip
⚫The microdrip chamber delivers 60 gtt (drops)/mL.
⚫This type of chamber is used if fluid will be infused
at a slow rate (<100 mL/hr).
⚫A microdrip chamber is also used if the solution contains
potent medication that must be titrated (e.g., in a critical care setting or pediatrics).
Macrodrip
⚫A macrodrip chamber is used to administer a solution that is thick or is to infuse rapidly (≥100
mL/hr).
⚫Check the tubing package to determine how many drops per milliliter are delivered; drop factor
may be 10, 15, or 20 gtt/mL).
Filters
⚫Filters, which provide protection by preventing particles from entering the client’s veins, are
used in IV lines to trap small particles (e.g., undissolved antibiotics, salt) or medications that
have precipitated in solution.
⚫Check agency policy regarding the use of filters.
⚫A 0.22-µm filter is used for most solutions, a 1.2-µm filter is used for solutions containing lipids
or albumin, and a special filter is used for blood components.
⚫Change the filter every 24 to 72 hours (depending on agency policy) to help prevent bacterial
growth.
Intermittent Infusion Sets
⚫This type of infusion set is used when intravascular accessibility is desired for intermittent
administration of medications by means of IV push or IV piggyback.
⚫An IV lock is attached to an intermittent infusion device.

⚫Patency is maintained through periodic flushing with NS. (“Sodium chloride” and “normal saline
solution” *a.k.a. NS+ are interchangeable.)
⚫When administering medication, flush the line with 1 to 2 mL (depending on agency policy) of
NS to confirm placement of the IV cannula; administer the prescribed medication, then flush the
cannula again with 1 to 2 mL (depending on agency policy) of NS to maintain patency.
Adding Medication to an Intravenous Bag
⚫Assess the compatibility of the medication and solution.
⚫Before adding any medication or solution to an IV bag, swab the access ports with 70% alcohol
or an equally effective solution as specified by agency policy.
⚫After adding medication to the IV bag, mix the contents of the bag from end to end several
times to disperse the medication before hanging the bag.
⚫Ensure that the medication can be mixed in soft plastic; some medications are absorbed into
plastic and should be mixed only in glass.
Electronic Intravenous Infusion Devices
⚫Electronic IV infusion devices, which are used to control the amount of fluid infusing, should be
used with central venous lines, arterial lines, parenteral nutrition infusions, and infusions
containing medications.
⚫A syringe pump is used when a small volume of medication is administered; the syringe that
contains the medication and solution fits into a pump set to deliver the medication at a
controlled rate.
⚫Patient-controlled analgesia (PCA) is a device that allows the client to self-administer IV
medication, generally an analgesic. The device is set to allow the client to administer a certain
number of bolus doses at set intervals, after which the pump “locks out” the client for an
appropriate period to help prevent overdose.
⚫Check electronic IV infusion devices frequently; although these devices are electronic, this does
not ensure that they are infusing solutions and medications correctly.
Epidural Catheter
⚫The epidural catheter is placed in the epidural space for the administration of analgesics; this
method of administration reduces the amount required to control pain and therefore reduces
the incidence and severity of side effects.
⚫Assess the client’s vital signs, level of consciousness, and motor and sensory function.
⚫Monitor the insertion site for signs of infection; ensure that the catheter is secured to the
client’€™s skin and that all connections are taped to prevent disconnection.
⚫Check the physician’s prescription regarding solution and medication administration.
⚫For continuous infusion, monitor the electronic infusion device for proper rate of flow.
⚫For bolus dose administration, follow the agency procedure for administering bolus doses.
⚫Aspiration is performed before medication is injected; if more than 1 mL of clear fluid or blood is
returned, do not inject the medication and instead notify the physician or anesthesiologist
immediately. (The catheter may have migrated into the subarachnoid space or a blood vessel.)
⚫Contraindications to the use of an epidural catheter and administration of epidural analgesia
include skeletal and spinal abnormalities, bleeding disorders, use of anticoagulants, history of
multiple abscesses, and sepsis.
Complications of Intravenous Therapy
Infection
⚫Maintain strict asepsis when caring for the IV site.
⚫Check fluid containers for cracks, leaks, cloudiness, and other evidence of contamination.
⚫Change tubing and site dressing at least every 72 hours or as specified by agency policy.
⚫Label IV site, bag or bottle, and tubing with the date and time to ensure that all are changed on
time in accordance with agency policy.
⚫Ensure that an IV solution does not hang for more than 24 hours.
⚫If infection occurs, discontinue the IV infusion, place a sterile cover on the venipuncture device
to enable a culture, if one is prescribed, and notify the physician.
⚫Prepare to obtain blood for cultures as prescribed if infection occurs.
⚫Restart an IV line in the opposite arm to differentiate sepsis (systemic infection) from local
infection at the IV site.
Tissue Damage
⚫Use a careful, gentle approach when applying a tourniquet.
⚫Avoid tapping the skin over the vein when starting an IV line.
⚫Monitor the skin for ecchymosis after penetrating it with the cannula.
⚫Assess the client for allergies to tape or dressing adhesives.
⚫Monitor the client for skin color changes, sloughing of the skin, and discomfort at the IV site.

⚫Notify the physician if tissue damage is suspected.
⚫Document the findings of assessment for tissue damage, its effects, and actions taken.
Phlebitis and Thrombophlebitis
⚫Use an IV cannula smaller than the vein and avoid very small veins when administering irritating
solutions.
⚫Avoid using the legs and feet as access areas for IV lines.
⚫Avoid venipuncture over areas of flexion.
⚫Securely anchor the cannula and a loop of tubing with tape.
⚫Use an armboard or a splint (per agency policy) if the client is restless or active.
⚫Change the venipuncture site at least every 72 hours.
⚫If phlebitis occurs, remove the IV device immediately and start a new IV line in the opposite
extremity.
⚫Notify the physician if phlebitis is suspected (warm, moist compresses may be prescribed).
⚫If thrombophlebitis occurs, do not irrigate the IV catheter; remove the IV line, notify the
physician, and start a new line in the opposite extremity.
Infiltration
⚫Avoid venipuncture over areas of flexion.
⚫Securely anchor the cannula and a loop of tubing with tape.
⚫Use an arm board or a splint if the client is restless or active.
⚫Assess the IV site for pain, edema, and coolness, comparing it with the same spot on the
opposite extremity.
⚫Monitor the IV rate for a decrease in or cessation of flow.
⚫If infiltration has occurred, remove the IV cannula immediately.
⚫Do not rub an infiltrated area, which could cause the development of a hematoma.
⚫If infiltration has occurred, elevate the extremity and apply moist compresses (warm or
cool, depending on the IV solution that was infusing and the physician’s prescription) over
the affected area.
Catheter Embolism
⚫Monitor the client for signs of catheter embolism, which occurs when the tip of a catheter
breaks off.
⚫Remove the catheter carefully.
⚫Inspect the catheter after removing it.

⚫If the catheter tip has broken off, place a tourniquet high on the limb of the IV site, notify the
physician immediately, prepare to obtain an x-ray, and prepare the client for surgery to remove
the catheter fragments, if this is prescribed.
Circulatory Overload
⚫Identify clients at risk for circulatory overload.
⚫Calculate the infusion rate and monitor it closely once the infusion has been started.
⚫Use an electronic infusion device and frequently check the drip rate or setting, particularly in
clients at risk for overload.
⚫Add a time strip to the IV bag or bottle.
⚫Monitor the client for signs of circulatory overload.
⚫If circulatory overload occurs, decrease the flow rate to a minimum (keep-vein-open rate),
elevate the head of the bed, keep the client warm, assess the client for pulmonary edema;
the physician is notified immediately.
Air Embolism
⚫Prime the tubing with fluid before use and watch for air bubbles in the tubing.
⚫Secure all connections.
⚫Replace IV fluid before the bag or bottle runs dry.
⚫Monitor the client for signs of air embolism; a loud churning sound over the precordium, a result
of air in the right ventricle, may also be heard.
⚫If air embolus is suspected, clamp the tubing, turn the client on the left side with the head of the
bed lowered (Trendelenburg position) to trap the air in the right atrium, and notify the
physician.
DOSE CALCULATIONS
Metric System
1 milligram (mg) = 1000 micrograms (mcg)
1 gram (g) = 1000 mg
1 kilogram (kg) = 1000 g
1 kg = 2.2 pounds (lb)
1 liter (L) = 1000 milliliters (mL)
Apothecary and Household Systems
1 ounce (oz) = 30 mL
1 tablespoon (T) = 15 mL
1 teaspoon (t) = 5 mL
15 drops (gtt) = 1 mL 1
1 quart = 1000 mL or 1 L
1 pint = 16 oz
16 oz = 1 lb

grain (gr 1) = 60 mg – (gr 1/150 = 0.4 mg)
Basic Formula
D x Q = X
A
D (desired) is the dosage the physician has prescribed.
A (available) is the dosage strength as stated on the medication label.
Q (quantity) is the volume in which the dosage strength is available (e.g., tablets, capsules, milliliters).
Ratio and Proportion
H (on hand) : V (vehicle) :: (=) D (desired dose) : X (unknown)
The left side of the :: (=) represents known quantities, the dose on hand ( ) and the vehicle ( ). The rightH V
side of the equation represents the desired dose ( ) and the unknown amount to be given ( ). Multiply D X
the means ( and ) and the extremes ( and ), then solve for X.V D H X
Other drug measures include the used for medications such as potassium, and milliequivalent (mEq), the
unit, used for medications such as heparin and insulin.
Calculating the Correct Dosage
⚫Although there is more than one way to calculate a medication dose, in this lesson the basic
formula and ratio and proportion methods are presented.
⚫If you have learned a different method of calculating doses, you may continue using that
method.
⚫When calculating a dose of an oral medication, check your calculation and then question the
prescription if the calculation calls .for more than three tablets
⚫When calculating a dose of a parenteral medication, check your calculation and then question
the prescription if the amount to be given is .larger than normal or seems excessive
⚫Be sure that all measures are in the same system and that all units are in the same size,
converting when necessary; carefully consider the reasonable amount of the medication that
should be administered.
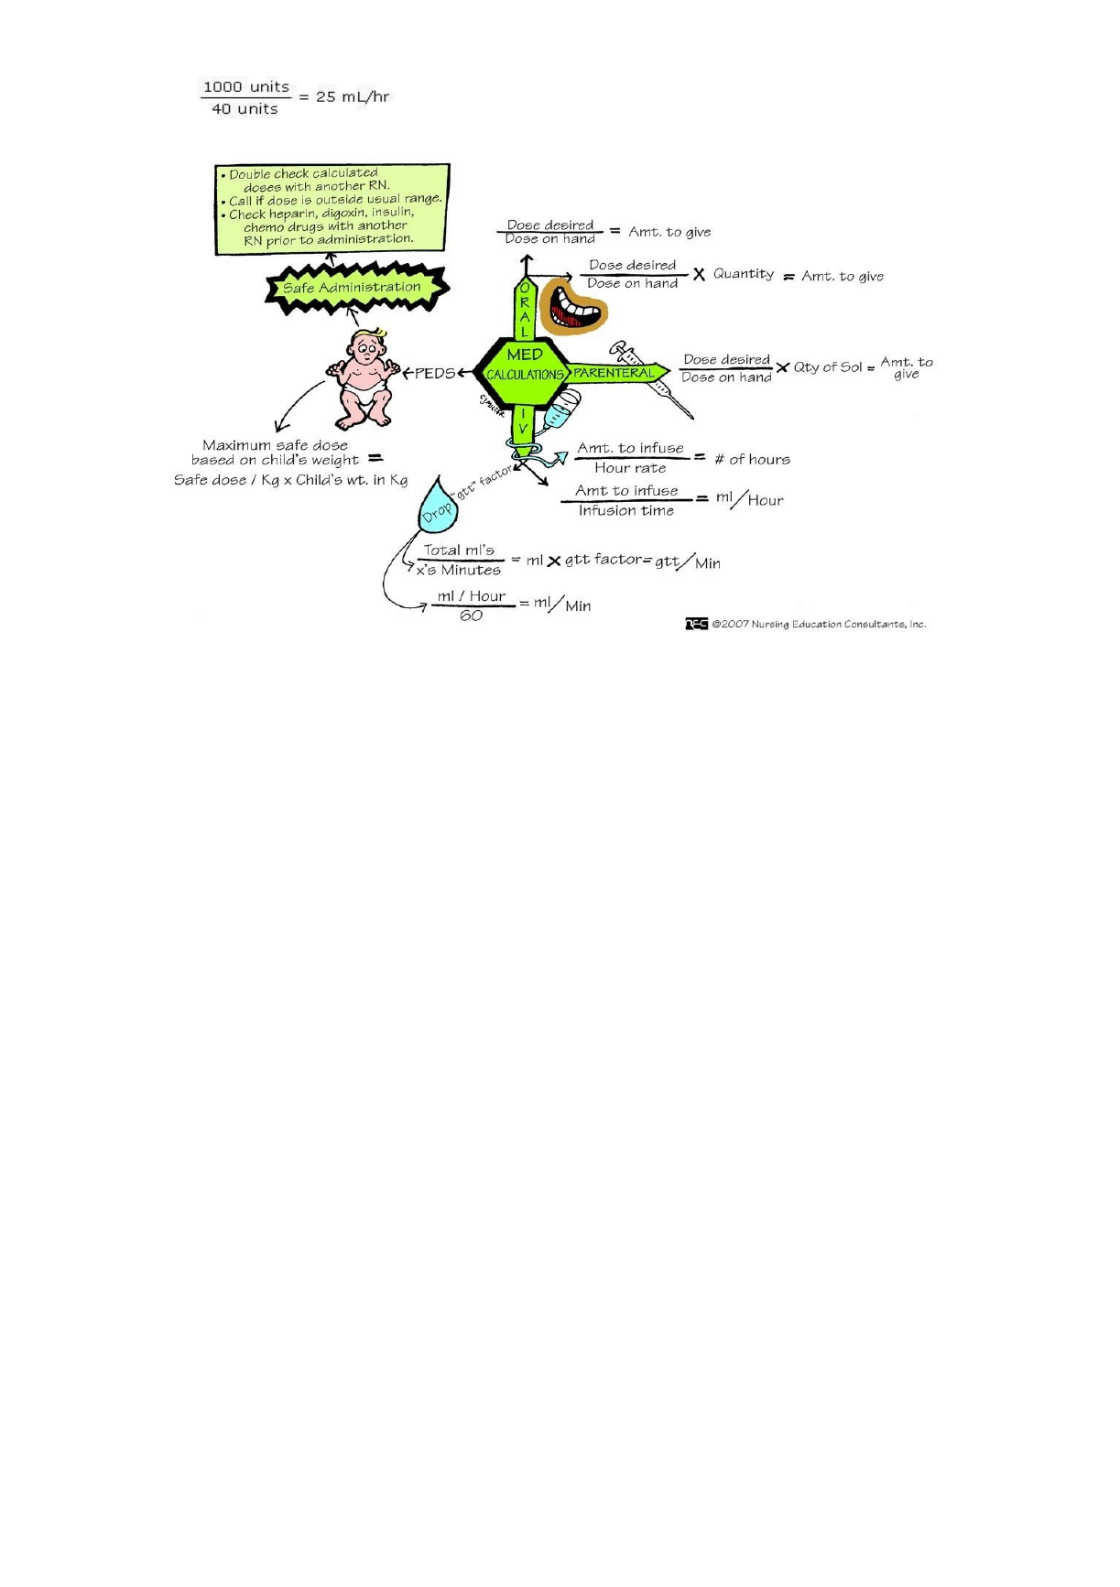
Formula for Flow Rate
Example: The physician prescribes 1000 mL normal saline solution to infuse over 8 hours. The drop
factor is 10 gtt/mL. Round answer to the nearest whole number.

If the Flow rate is asked in mL/h, the formula doesn’t include the drop factor, therefore, the following
formula will be used:
Total Volume (mL)
= mL/h
Time (hr)
It has to be considered that 1 hr is the unity,
therefore: 15’=0.25 hr
30’=0.5 hr
45’=0.75 hr
60’= 1 hr
Formula for Infusion Time
Example: The physician prescribes 1000 mL to infuse at 100 mL per hour.
Infusions Ordered by Unit Dose per Hour
Steps
⚫Calculate the amount of medication per 1 mL.
⚫Calculate the infusion rate or milliliters per hour.
Example
Prescription: Heparin sodium continuous IV infusion at 1000 units/hr
Available: IV bag of 500 mL D W with 20,000 units of heparin sodium
5
Question: How many milliliters per hour are required for the correct dose?
Step 1: Calculate the amount of medication (units) per milliliter (mL).
Step 2: Calculate milliliters per hour.
BLOOD AND BLOOD COMPONENTS
Blood Components
Donor blood is converted into various products, including:
Packed red blood cells (RBCs)
Whole blood
Platelets
Fresh frozen plasma
Albumin
Cryoprecipitates
Types of Blood Donation
⚫An donation reduces the risk of disease transmission and potential transfusionautologous
complications but is not an option for a client with leukemia or bacteremia.
⚫Blood obtained through may need to undergo “washing,” a process that removesblood salvage
tissue debris, before being infused.
⚫Infusion of blood taken from a does not reduce the risk of bloodbornedesignated donor
infection, but recipients often feel more comfortable about taking blood from a donor they
know and approve of.
Determining Compatibility
⚫Client blood samples are drawn and labeled at the bedside; the client is asked to state his or her
name, which is compared with the name on the client's identification band or bracelet.
⚫The recipient’s ABO and Rh types are identified.
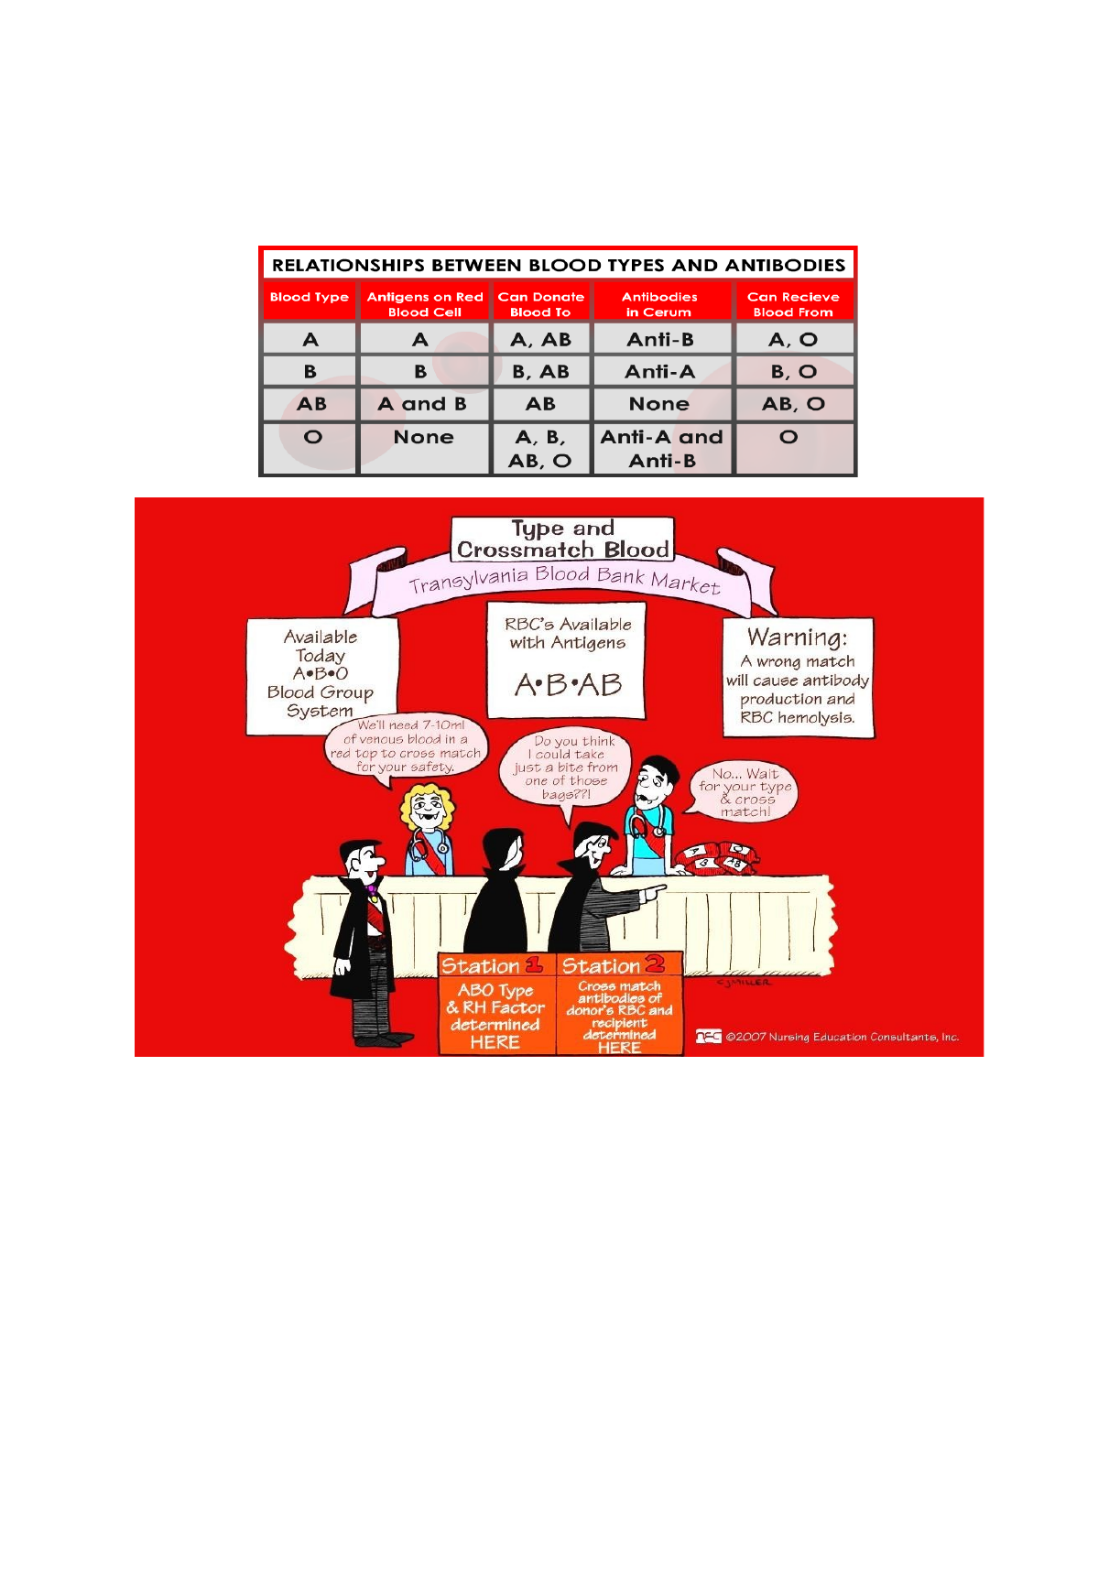
⚫An antibody screen is performed to determine whether antibodies other than anti-A and anti-B
are present.
⚫Crossmatching is performed: Donor red blood cells (RBCs) are combined with the recipient’s
serum and Coombs’ serum. The crossmatch is compatible if no RBC agglutination occurs.
⚫The universal RBC donor is O-negative; the universal recipient is AB-positive.
Transfusion Equipment
Infusion Controllers and Pumps
⚫Infusion controllers and pumps may be used to administer blood products if they are designed
to function with opaque solutions; however, the negative pressure exerted by the cassette of
the machine may cause hemolysis of RBCs.
⚫Always consult manufacturer guidelines for the controller or pump before using it.
⚫Special manual pressure cuffs may be used to increase the flow rate, but pressure should not
exceed 300 mm Hg.

⚫Because they do not exert uniform pressure against all parts of the bag, standard
sphygmomanometer cuffs should not be used to increase the flow rate.
Blood Warmers
⚫A blood warmer may be used to and adverse reactions when several unitsprevent hypothermia
of blood are being administered.
⚫Special warmers have been specifically tested and approved for this use, and only such devices
should be employed. Never warm blood products in a microwave or in hot water.
Nursing Precautions
⚫A large volume of refrigerated blood infused rapidly through a central catheter into the heart
can cause .cardiac dysrhythmias
⚫No fluid other than solution should be added to blood components, nor shouldnormal saline
medications be added to a blood transfusion.
⚫As a means of reducing the risk of septicemia, infusion time (of 1 unit) should not exceed 4
hours and the administration set should be changed every 4 hours or in accordance with agency
policy.
⚫Always check the blood bag for the date of expiration; components expire at midnight on the
day marked on the bag unless otherwise specified.
⚫Inspect the blood bag for leaks, abnormal color, clots, air, and bubbles.
⚫Blood must be administered of its being received from the blood bank; this iswithin 30 minutes
the maximal allowable time out of monitored storage.
⚫Never store blood in a refrigerator other than those used in blood banks; once removed from
the blood bank, if the blood is not administered within 30 minutes, return it to the blood bank.
⚫The recommended rate of infusion varies with the blood component being transfused and the
client's condition, but generally blood is infused as quickly as the client's condition will allow.
⚫Blood products containing few RBCs, such as , may be infused rapidly (over 15 to 30platelets
minutes), but care should be taken to avoid circulatory overload.
⚫Vital signs and lung sounds should be assessed before the transfusion, again after the first 15
minutes of transfusion, and every hour until 1 hour has passed since the transfusion was
completed.
Client Identity and Compatibility
⚫The most critical steps in the transfusion process are confirmation of product compatibility and
verification of client identity.
⚫Two licensed nurses must check the physician’s prescription, the client’s identity, and the
client’s ID band and number, verifying that the name and number are identical to those on the
blood component tag.
⚫At the bedside, the client is asked to state his or her name, which the nurse compares with the
name on the client’s ID band.

⚫The blood bag tag and label and the blood requisition form are assessed to ensure that the
client’s ABO and Rh types are compatible with the blood product.
⚫If inconsistencies are noted during verification, the blood bank is notified.
Client Assessment
⚫Assess the client for cultural or religious beliefs regarding blood transfusions (e.g., a Jehovah’s
Witness cannot receive blood or blood products, because members of this faith believe that
receipt of a blood transfusion has eternal consequences).
⚫Ensure that has been obtained.informed consent
⚫Determine whether the client has ever experienced a reaction to a blood transfusion.
⚫Check the client’s vital signs; assess renal, circulatory, and respiratory status and the client’s
ability to tolerate intravenous (IV) fluids.
⚫If the client’s temperature is increased, notify the physician before beginning the transfusion;
fever may be a reason to delay the transfusion and could mask symptoms of an acute
transfusion reaction.
Administering a Transfusion
⚫Maintain standard precautions.
⚫Insert an IV line and infuse normal saline solution, maintaining flow at a keep-vein-open rate.
⚫To help prevent circulatory overload, always check the bag for its volume before starting the
infusion.
⚫Pre-medicate the client with acetaminophen (Tylenol) or diphenhydramine hydrochloride
(Benadryl) as prescribed if the client has a history of adverse reactions.
⚫If prescribed, oral medications used to prevent an adverse reaction should be administered 30
minutes before the transfusion is started; IV medications should be given immediately before
the transfusion is started.
⚫Instruct the client to report any unusual sensations or emotions immediately.
⚫Determine the rate of infusion by consulting the physician’s prescription or, if not specified,
agency policy.
⚫Begin the transfusion slowly during theand monitor the client closely; if no reaction is noted
first 15 minutes, the flow may be increased to the prescribed rate.
⚫During the transfusion, monitor the client for signs and symptoms of transfusion reaction; the
first 15 minutes of the transfusion are the most critical, and the nurse must stay with client.
⚫A major ABO incompatibility or severe allergic reaction will usually become evident during
infusion of the first 50 mL of the transfusion.
⚫Document the client’s tolerance of the administration of the blood product.
⚫Monitor appropriate laboratory values and document the effectiveness of treatment.
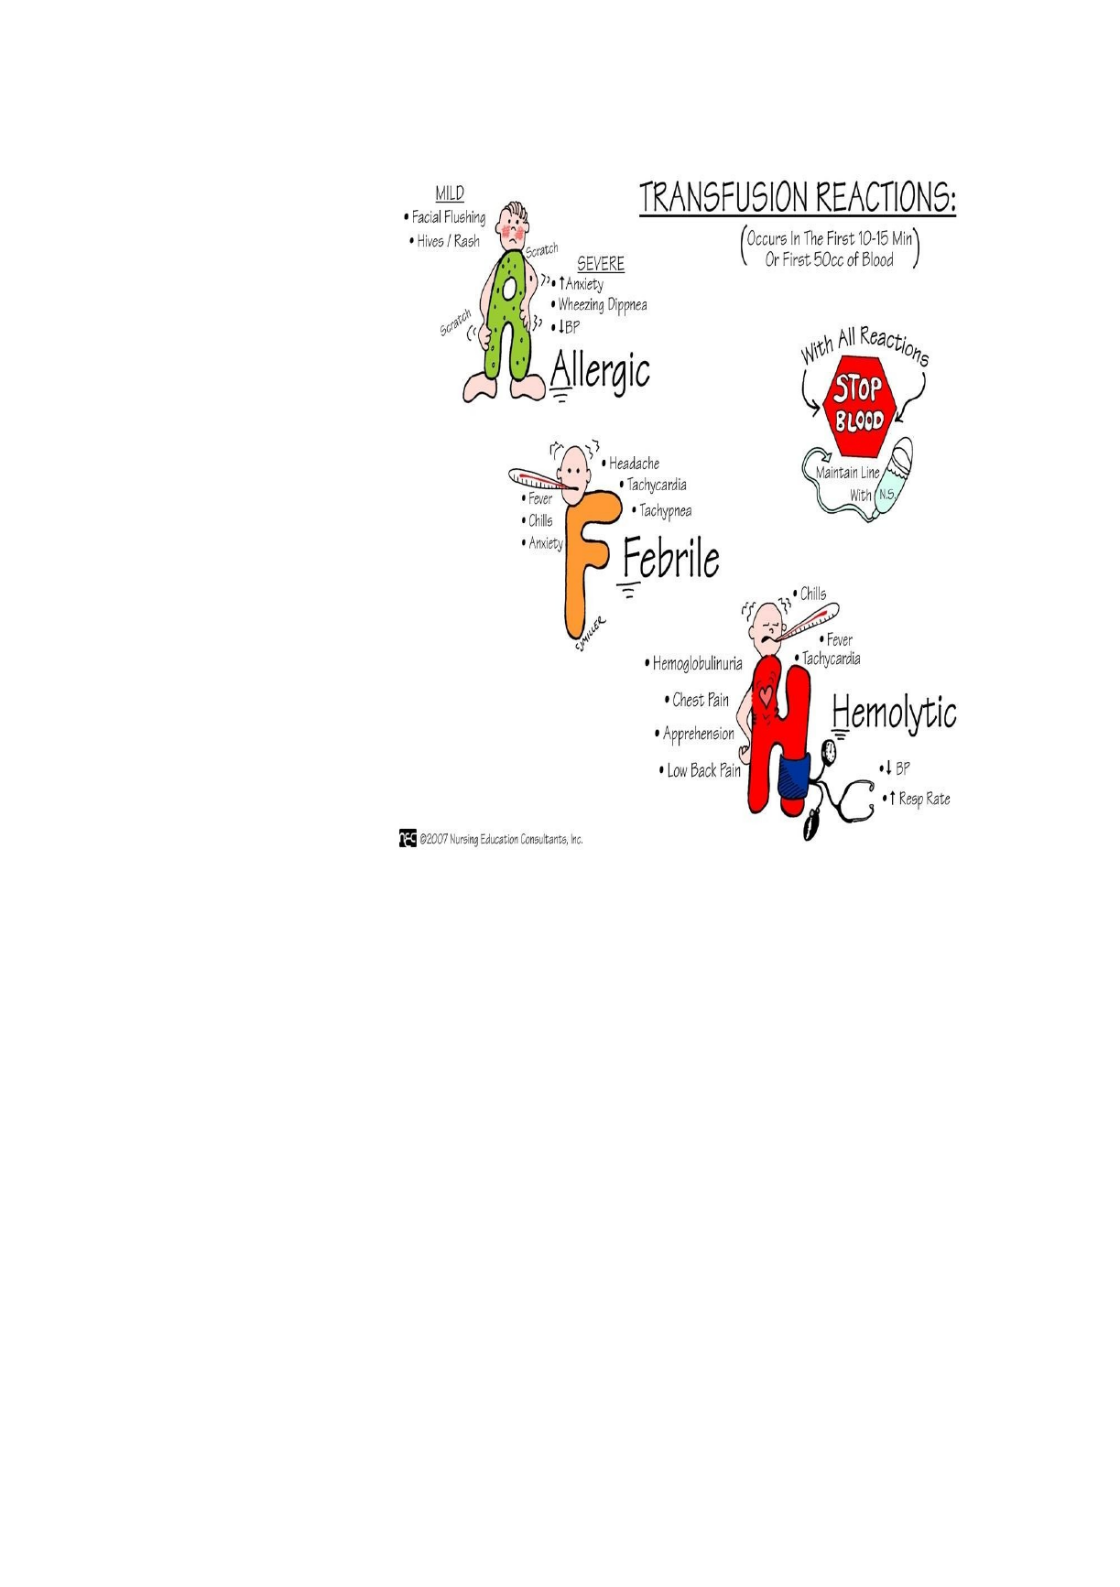
An adverse and potentially life-threatening event that occurs when a client receives blood that is
incompatible with his or her blood type or Rh type.
Signs may occur during the infusion or days or even years afterward as a delayed reaction.
Immediate Signs
⚫Chills and diaphoresis
⚫Muscle aches, back pain, chest pain
⚫Rashes, hives, itching, swelling
⚫Rapid, thready pulse
⚫Dyspnea, cough, wheezing
⚫Pallor and cyanosis
⚫Apprehension
⚫Tingling and numbness
⚫Headache
⚫Nausea and vomiting,
⚫Abdominal cramping
⚫Diarrhea
Delayed Signs
⚫Fever
⚫Mild jaundice
⚫Decreased hematocrit
Interventions
⚫If a transfusion reaction occurs, stop the transfusion, change the IV tubing down to the IV site,
and keep the IV line open with 0.9% normal saline solution.
⚫Notify the physician and the blood bank.
⚫Remain with the client, observing signs and symptoms and checking vital signs as often as every
5 minutes.
⚫Prepare to administer emergency medications (e.g., antihistamines, corticosteroids,
vasopressors) and fluids as prescribed.
⚫Obtain blood and urine specimens for laboratory studies. (Free hemoglobin in the urine
indicates that hemolysis of RBCs has occurred.)
⚫Return the blood bag, tubing, attached labels, and tranfusion record to the blood bank.

Chemotherapy Drugs

Bone marrow suppression (monitor bleeding, avoid IM injections and rectal temperatures, press
venipuncture sites);
nausea and vomiting (monitor appetite and nutrition, I and O; prophylactic antiemetics; small,
frequent meals);
altered immunologic response (prevent infection and report early signs);
impaired oral mucous membrane; stomatitis (monitor oral hygiene; avoid hot, spicy foods).
Administer antifungals and anesthetics as ordered.
For fatigue (rest, energy conservation teaching).
Extravasation (Vesicant)
Most common nursing intervention is PREVENTION!
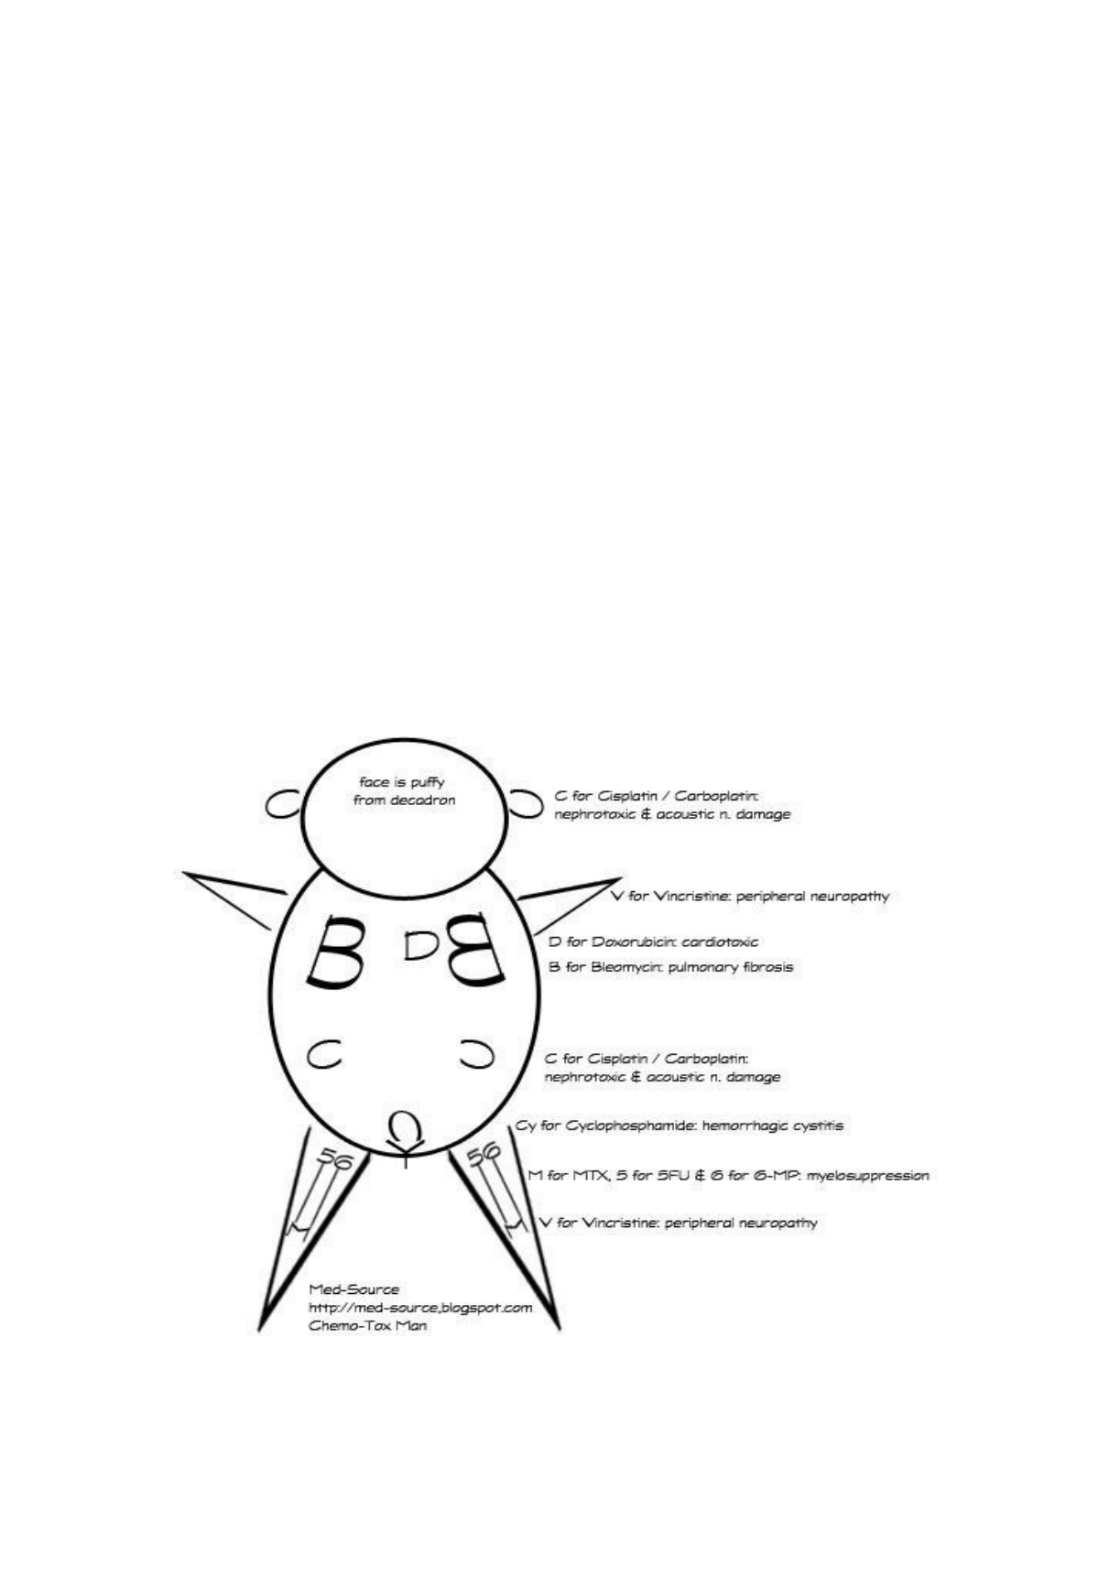
Cisplatin, Procarbozine
OTOTOXIC, NEPHROTOXIC, INFERTILITY, HY[ERURICEMIA
Nursing implications:
HYDRATION prior to therapy;
monitor I & O,
maintaining at least 100 ml/hr output to reduce risk of nephrotoxicity;
encourage fluid intake of 2000- 3000 ml in 24 hours to reduce uric acid.
Doxorubicin
Side effects:
CARDIOTOXIC (Dilated Cardiomyopathy)
Cross allergy with Penicillin
Nursing implications:
assess for history of penicillin allergy
rotate IV sites;
probenecid will decrease excretion and increase blood levels;
may potentiate effects of anticoagulants
Methotrexate
Adverse reaction:
BONE MARROW SUPRESSION!: anemia, leukopenia, thrombocytopenia
INTERACTION: salicylates, NSAIDS, phenytoin, and sulfonylurias
Nursing implications-:
assess for signs of bone marrow depression; petechiae, sore throat, fatigue, unusual
bleeding, (bruising).
patients with impaired lifer or renal function , infants, children, and elderly are at
greatest risk of developing adverse effects.
Vincristine
Adverse reactions:
ASCENDING PERIPHERAL NEUROPATHY!
Increases uric acid
Vesicant
Nursing implications
monitor vital signs nerological status,
I & O; assess infusion site frequently,
assess nutritional status,
monitor for s/s of gout ( increased uric acid, joint pain, and edema);
encourage at least 2 liters of fluid intake.

Obstetrics
•Categories
•A- medication are considered safe during pregnancy
•B- animal studies have not shown a risk to fetus, but no controlled studies in pregnant women
•C- animal studies have shown adverse effects on fetus, but no adequate studies have been conducted
on humans.
•D- the drug may cause risk to human fetus, but the potential benefits of use in pregnant women may
be acceptable (as in a life-threatening)
•X- studies in animals or humans show fetal abnormalities. The risks clearly outweigh any potential
benefit.
Antimicrobials
Need to be given at regular intervals to maintain therapeutic blood levels and prevent development
of resistant strains of bacteria.
Peak – 1 hour after IM or ½ hour after IV
Trough - just before the next dose
Superinfection- occurs when normal bacterial flora are changed by the use of antibiotic, This result in
growth
Antibiotics/Anti-infectives
Therapeutic effect
•Treatment an prophylaxis of various bacterial infections
•Kill or inhibit growth of susceptible pathogenic bacteria
•Not active against virus or fungi
•Sub-divided into categories based on chemical similarities and antimicrobial
spectrum
Contraindication
•Known hypersensitivity
•Cross-sensitivity among related agents may occur
Aminoglycosides
Uses- gram negative bacterial infections
•Adverse effects
•OTOTOXICITY, NEPHROTOXICITY, superinfection, photosensitivity with topical use
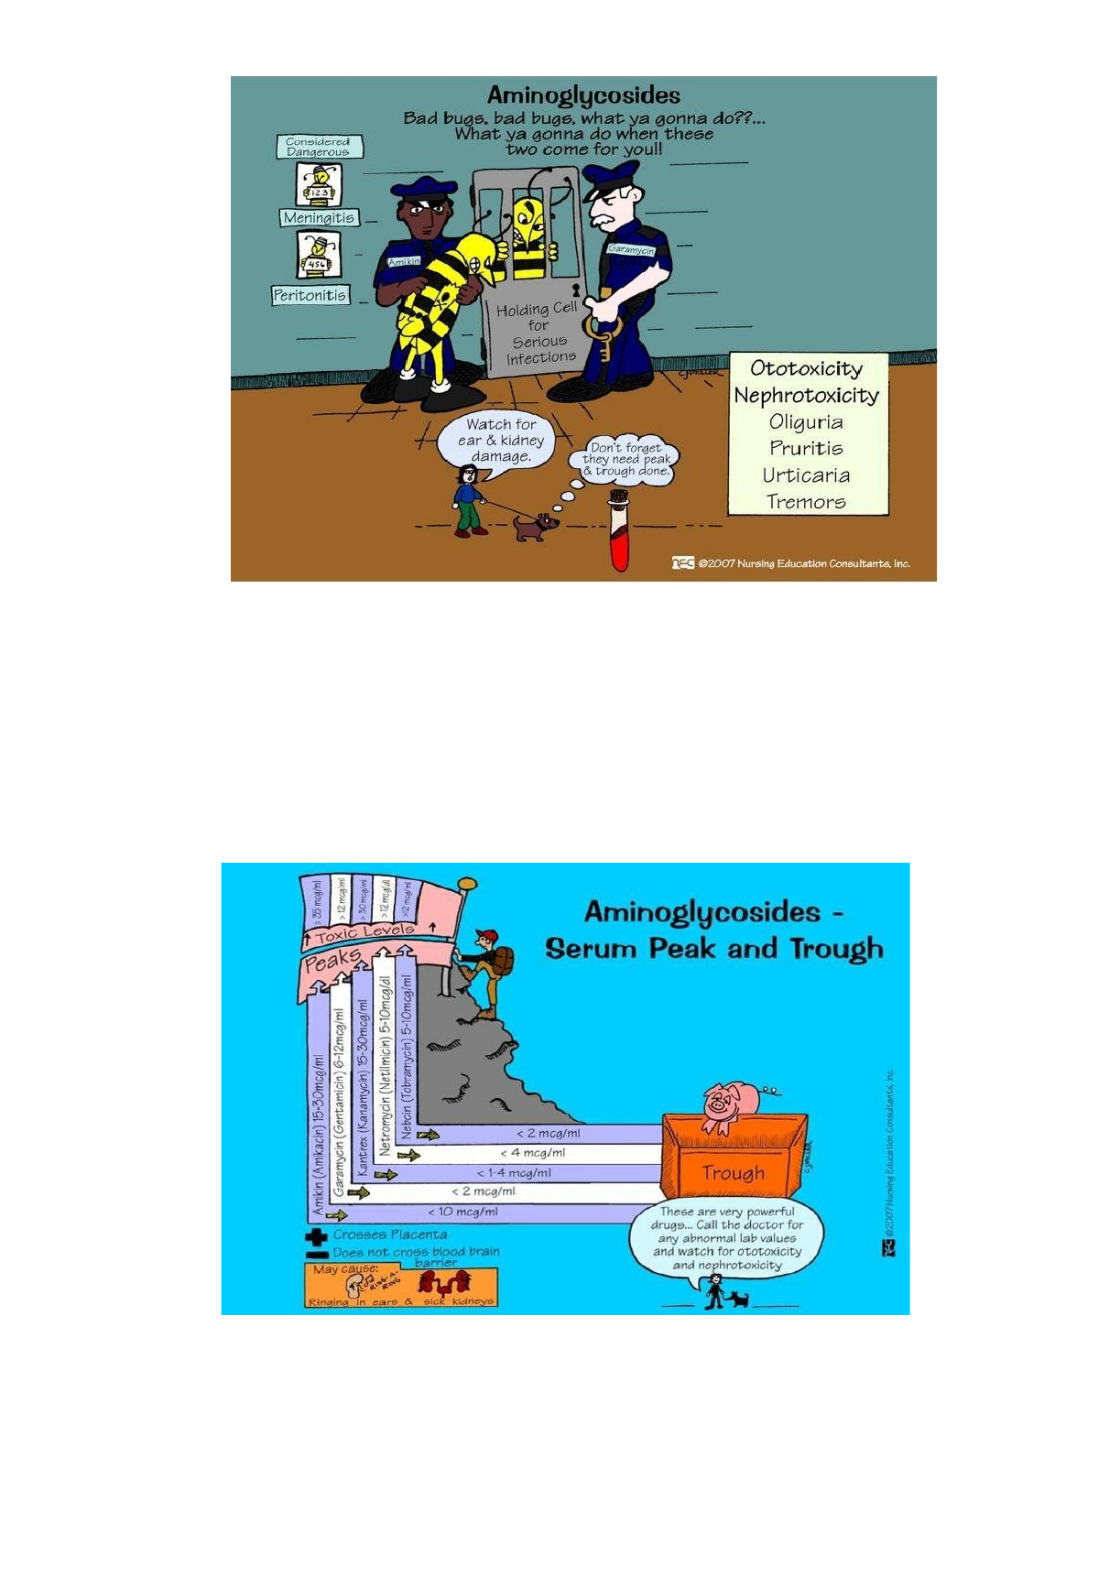
•Nursing Implications
•MONITOR RENAL FUNCTION TESTS AND I/O
•ASSESS FOR HEARING LOSS and balance.
•Monitor therapeutic levels
•Maintain adequate hydration
•Avoid sunlight
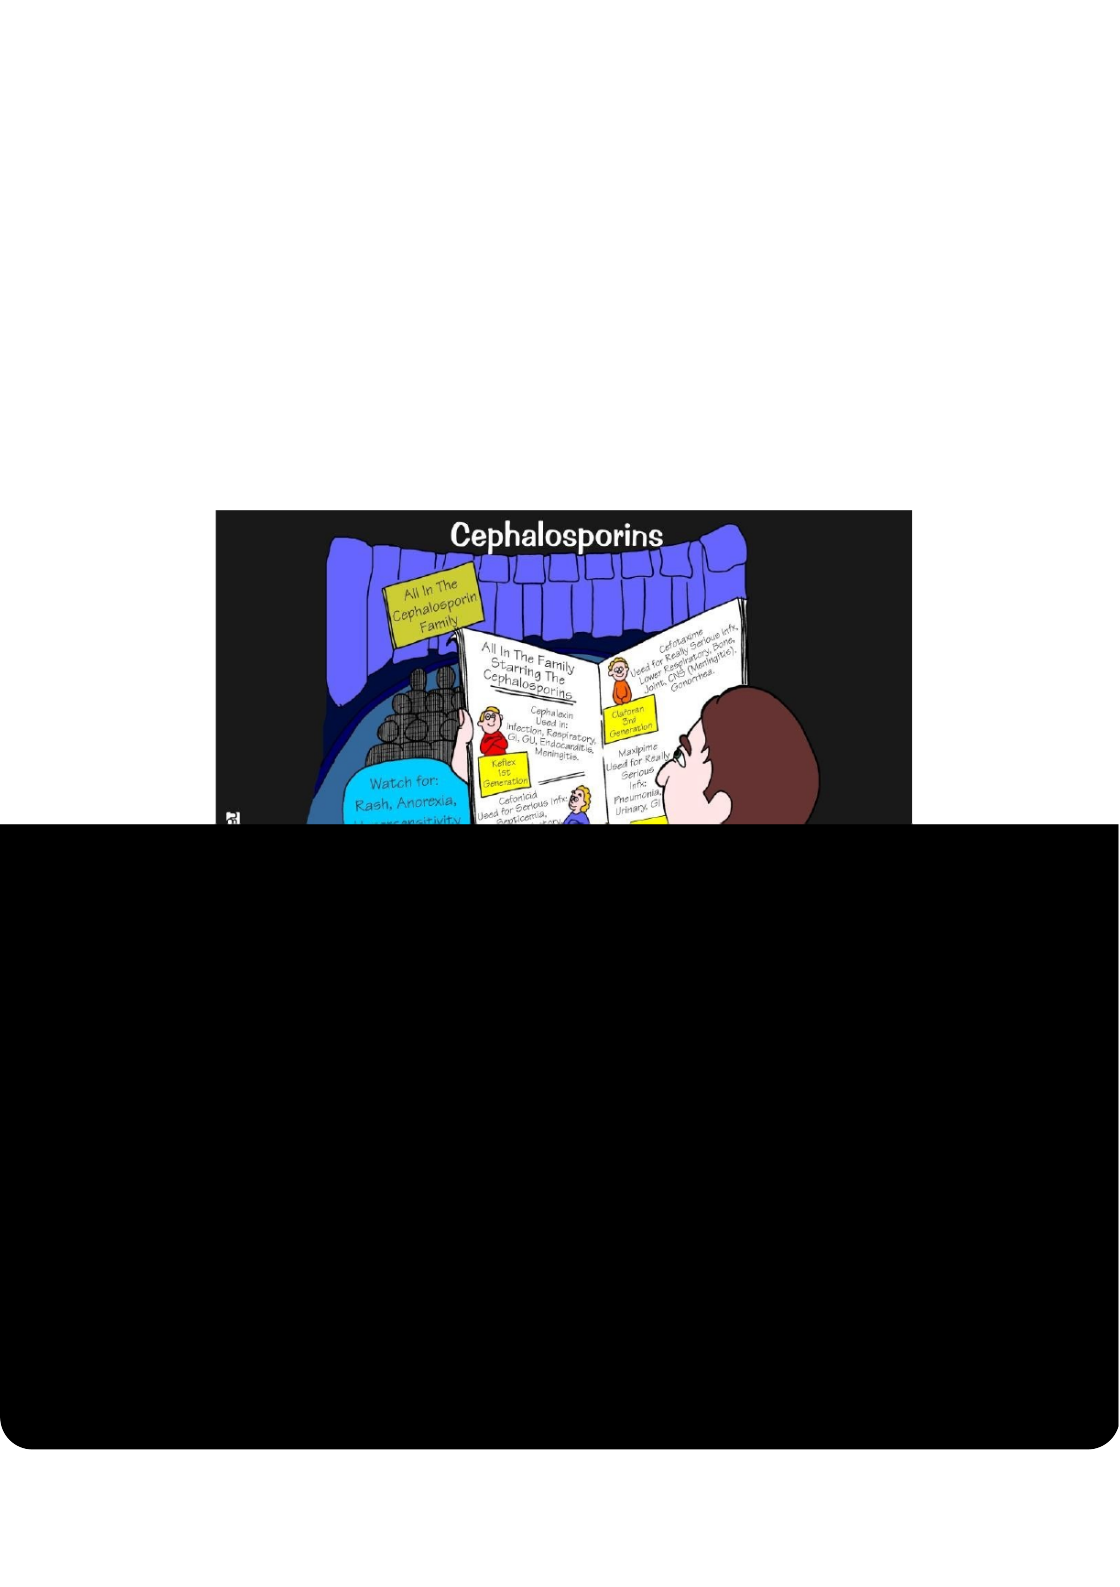
Cephalosporins
Uses: skin infection, pneumonia, otitis media
•Adverse effects
•PSEUDOMEMBRANOUS COLITIS,
•N/V/diarrhea, cramps, nephrotoxicity, rashes, superinfection, anaphylaxis, phlebitis, at
IV site
•Nursing Implications
•ASSESS FOR HX OF PENICILLIN ALLERGY, POTENTIAL CROSS SENSITIVITY,
•rotate IV sites,
•Probenecid will decrease excretion and increase blood levels, may potentiate
effects of anticoagulants.
Chloramphenical- chloromycetin
Uses: Management of the following serious infections when less toxic agents cannot be used: skin, soft
tissue infections, CNS infections, bacteremia, Ophthalmic-local infections
Adverse effects:
•BONE MARROW DEPRESSION, and GRAY SYNDROME IN NEWBORNS.
•Death due to baby’s immature liver function. Bitter taste after IV administration.
Nursing Implications
⮞ Assess for s/s of bone marrow depression
⮞ Patients with impaired liver or renal function, infants, children, and elderly are at
greatest risk of developing adverse effects.
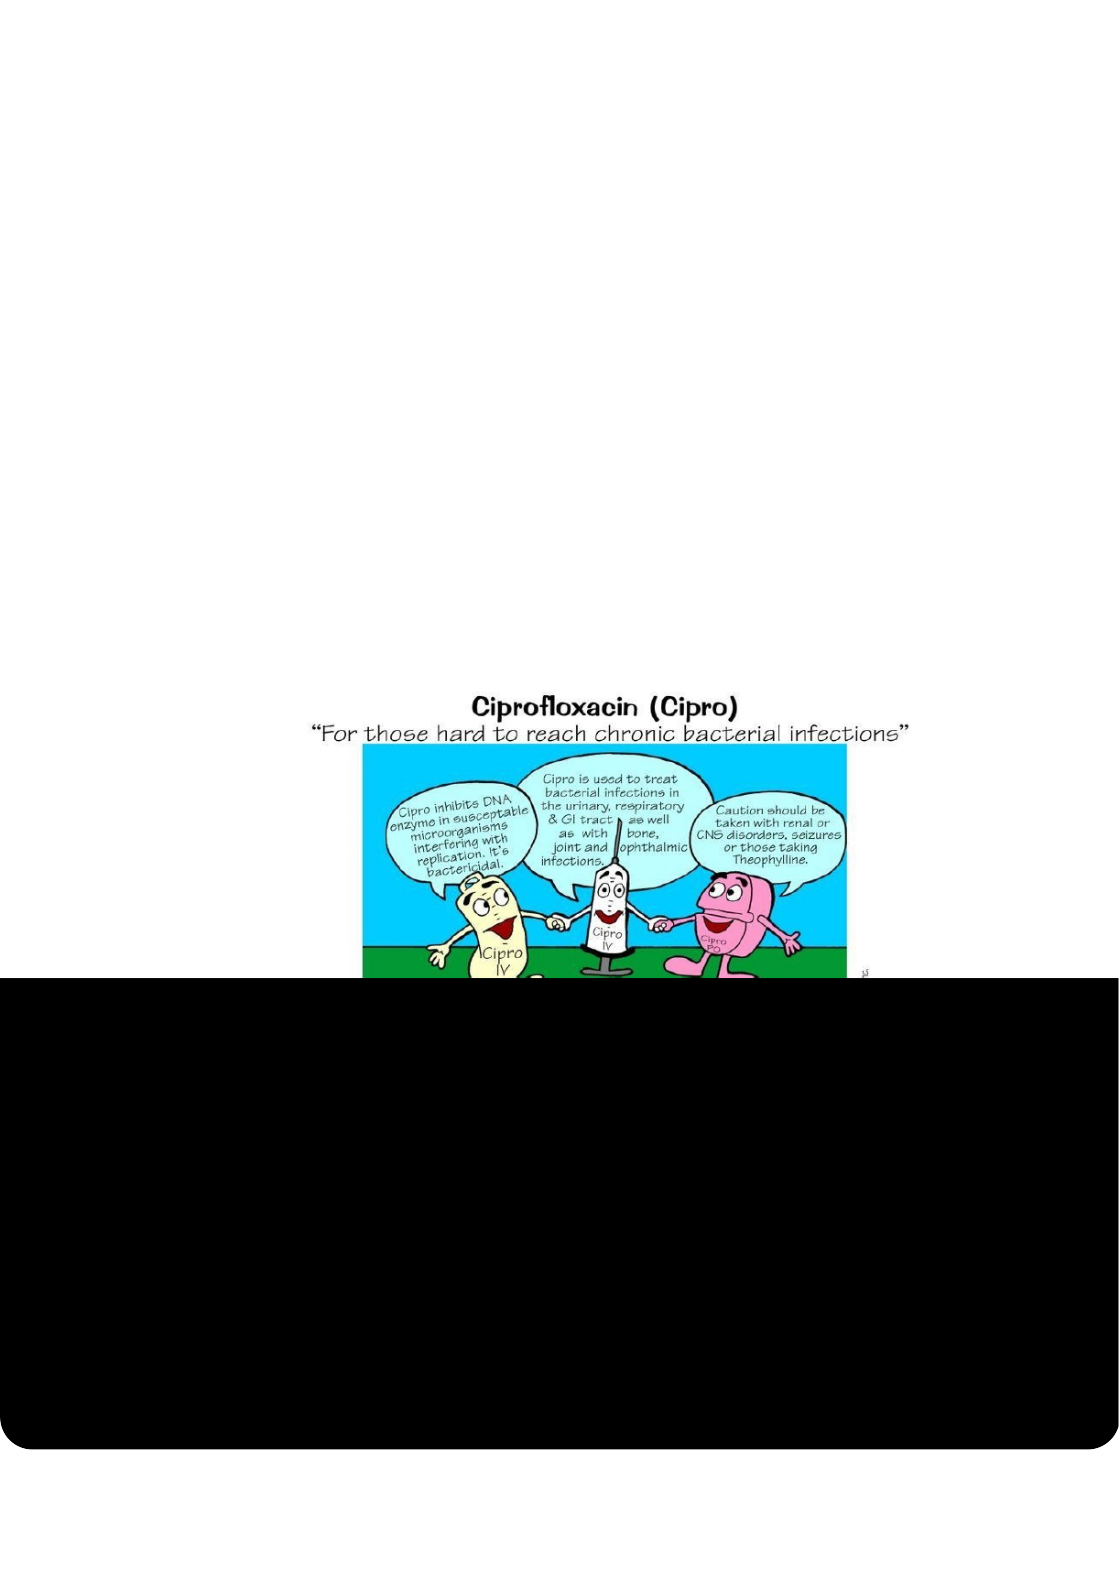
Floroquinolones
- ciprofloxacin, levofloxacin, norfloxacin
•Uses
Treatment of urinary tract and gynecologic, gonorrhea, prostatitis, respiratory
infections, skin, bone and joint; infectious diarrhea, perioperative prophylaxis before
transurethral or colorectal procedures, febrile neutropenia
Adverse effects
PHOTOSENSITIVITY, TENDON RUPTURE, dizziness
Nursing Implications
Mils and yogurt decrease absorption, antacids or meds with Irion or zinc decrease
absorption,
maintain fluid intake 1500-2000 ml/day,
IV over 60 minutes, may cause dizziness,
pt. to avoid sunlight or use sunscreen
Macrolides
Azithromycin, Clarithromycin, Erythromycin
Uses
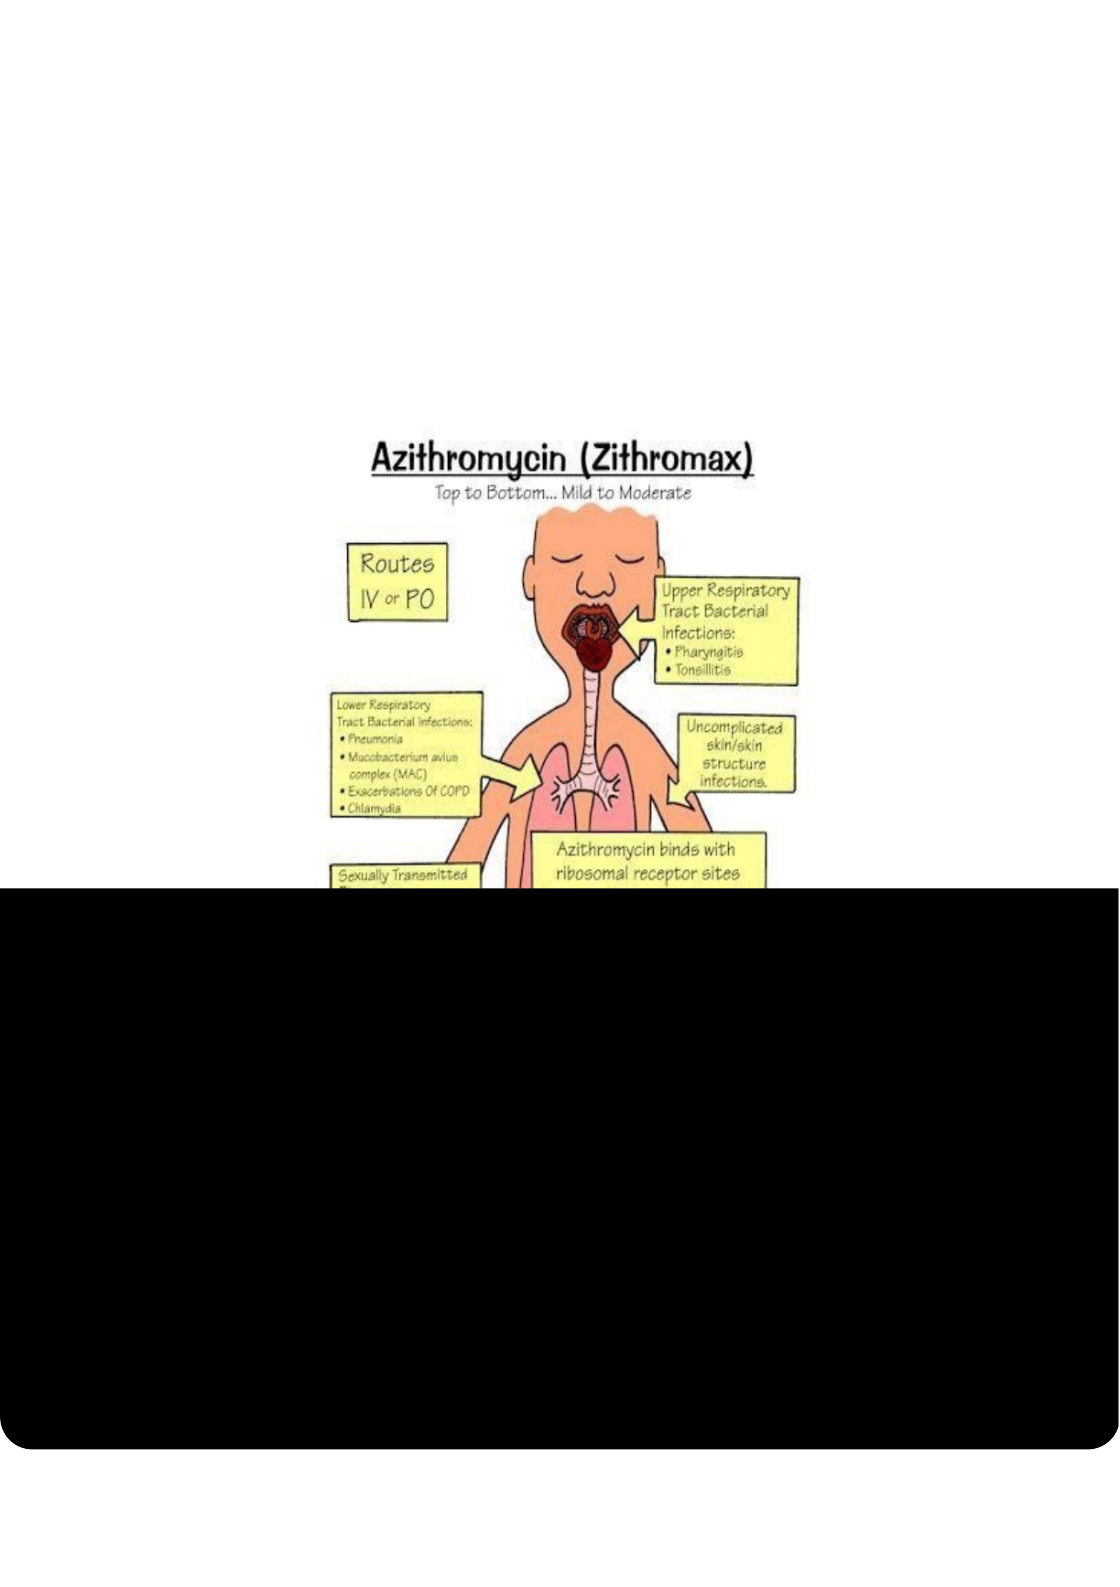
⮞ Upper and lower respiratory infections; otitis media, used for persons with penicillin allergy, when
penicillin is most appropriate choice
Adverse effects
⮞ N/V/D, Abdominal Pain, hepatotoxicity, ototoxicity, phlebitis at IV site, rash
•Nursing Implications
⮞ Don not crush enteric coated tablets,
⮞ non-coated tables best absorption on empty stomach,
⮞administer IV slowly to avoid phlebitis,
⮞ Give deeply IM in large muscle
Penicillins
Ampicillin, oxacillin
Uses

⮞ Treatment of a wide variety of infections; pneumococcal pneumonia, streptococcal
pharyngitis, syphilis, gonorrhea, enterococcal infections, prevention of rheumatic fever
Adverse effects
⮞ Epigastric distress, N/V/diarrhea, rashes, uticaria, pain at IM site, phlebitis at IV site,
superinfection, anaphylaxis
Nursing Implications
assess for previous reactions to penicillin and cephalosporin,
oral meds given on empty stomach,
monitor CBC, BUN and creatinine.
Sulfonamides
cotrimoxazole, sulfisoxazole
Uses
⮞ UTI, otitis media, pneumo-cystis carinii pneumonia
Adverse effects
⮞ STEVEN JOHNSON SYNDROME, PHOTOSENSITIVITY, agranulocytosis, aplastic anemia,
bleeding, crystalluria, superinfections.
•Nursing Implications
⮞ Assess IV site frequently for phlebitis
⮞ Monitor I/O 1200 to 1500 ml/day to prevent crytalluria and stone formation
⮞ Caution patient to use sunscreen, caution patient about contraceptives, monitor renal and
hepatic function

Tetracyclines
doxycycline, tetracycline, minocycline
Uses:
chlamydia, mycoplasma, acne, rickettsia, doxycycline- treatment of lime’s disease
Adverse effects:
•PHOTOSENSITIVITY, hepatotoxicity, chelating to teeth and new bone, TERATOGENIC.
Nursing Implications
⮞ Contraindicated in as drugPREGNANT, LACTATING WOMEN AND CHILDREN LESS THAN 8
binds to calcium in teeth and new bone growth.
⮞ Caution patient to use N, avoid taking with dairy products, antacids as calcium SUNSCREE
decreases absorption, and administer 1 hour before or 1 hour after meals.
Vancomycin
•Used for the treatment of potentially life threatening infections when less toxic anti-infectives is
contraindicated, Particularly useful in staph infection, pseudomembranous colitis
Adverse effects
⮞ Mainly associated with IV administration
⮞ Unpleasant taste,

⮞ OTOTOXICITY, NEPHROTOXICITY,
⮞ phlebitis, hypotension, back and neck pain,
⮞ RED MAN SYNDROME
•Nursing Implications
⮞ Monitor IV, B.P., I/O, cloudy or pink urine may be a sign of nephrotoxicity, nomitor bowel
status throughout therapy, monitor for auditory symptoms
Antivirals
acyclovir, amantadine
Therapeutic effect- inhibit viral replication or prevent penetration of the virus into the host cell,
management of herpes virus and chicken pox, prevention of influenza A viral infections, treatment of
ophthalmic viral infections and cytomegalovirus retinitis
Adverse reaction
⮞ NEPHROTOXICITY, dizziness, headache, diarrhea, nausea, vomiting, pain, phlebitis at IV site.
•Nursing implications
⮞ Assess for s/s of infection before and throughout therapy; opthamlmic, topical
⮞ Administer round the clock, complete full course of therapy, advise that transmission of the
virus is still possible
Antihypertensive and Cardiovascular Drugs
ACE inhibitors
Captopril, Enalapril, Lisinopril
Prevents production of angiotensin II, a potent vasoconstrictor that increases blood pressure. Uses- used
alone or with other agents in the management of hypertension and CHF.

Adverse reactions:
use cautiously in patient with renal or hepatic impairment; DRY COUGH
Hypotension
HYPERKALEMIA
Nursing implications
monitor BP and pulse frequently during initial therapy, monitor weight and assess
patient for resolution of fluid overload; monitor BUN, creatinine, and electrolyte levels
Beta blockers – OLOL
⚫Side effects: Bronchospasm, postural hypotension.
⚫Propranolol: (Continuous doses): Hyperthyroidism (Graves disease) & pheochromocytoma.
⚫Disadvantage: Non adherence.
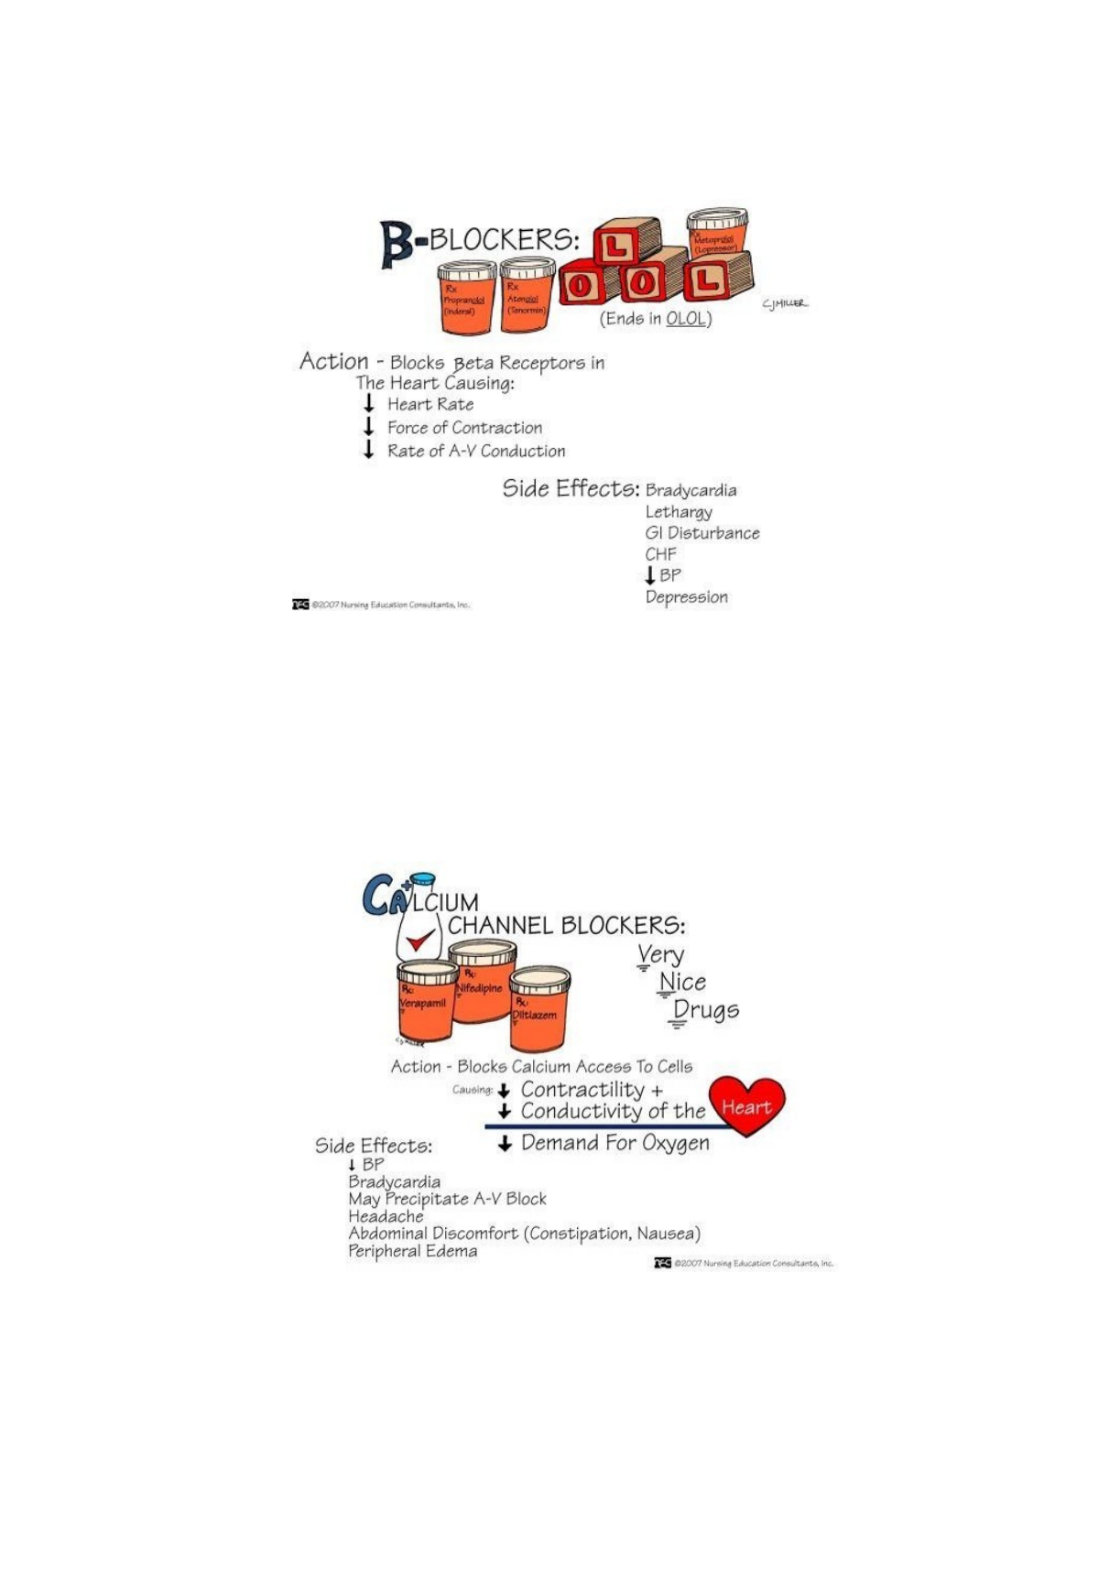
⚫Atenolol: (One dose daily):HTN, tachycardia.
⚫Teaching: HTN, inotropic negative (Check pulse > 60 before dose)
⚫Glaucoma optic drops: Timolol (Timoptic), betaxolol (betoptic). Close eye inner cantus 1-2 min
to avoid systemic absorption.
CALCIUM CHANNEL BLOCKERS:
⚫Suffix: DIPINE
⚫Very Nice Drugs: Verapamil, Nifedipine, Diltiazem
⚫Verapamil: in serious conditions.
⚫Diltiazem: Ambulatory, first line in African-Americans HTN.
⚫Dipines: Prinzmetal angina, Raynaud phenomenon (Lupus, scleroderma)
⚫Teaching: Peripheral edema, postural hypotension, avoid drinking grapefruit drug.
Anti-anginals
DRUG USES ADVERSE EFFECTS
NITRATES- DILATE CORONARY
ARTERIES AND CAUSE SYSTEMIC
VASODIALTION
USED IN TREATMETN OAND
PROPHYLAXIS OF ANGINA
PECTORIS. Only one nitrate may
be used in acute treatment of
angina pectoris attacks.
Given sublingual, buccal,
transdermal, IV for acute
treatment; PO (extended
release.
Dizziness, headache,
hypotension, tachycardia
Beta-adrenergic blockers
Decreases myocardial oxygen
consumption by slowing heart
rate: Atenolol, propranolol
Used prophylactically in long
term management of angina:
can be given PO or IV
Fatigue, weakness, bradycardia,
bronchospasm, dizziness,
hypotension, pulmonary
edema/CHF, constipation,
hypoglycemia
Calcium channel blockers:
Coronary vasodilatation with
decrease in frequency and
severity of angina: Amlodipine,
Diltiazem
Used prophylactically in long-
term management of angina: PO
Headache, fatigue, constipation,
hypotension, bradycardia,
arrhythmias, serum digoxin
levels may be increased
Nursing Implications
•Assess location, duration. Intensity and precipitating factors of patent's anginal pain
•Monitor BP and pulse throughout therapy
•Monitor I & O, daily weights for signs of CHF
•Instruct patient on use of nitrates for angina attack
•Caution patient to change position slowly to avoid orthostatic hypotension
•Caution patient to avoid alcohol

•Assess chest pain-PQRST
•Provoked by
•Quality
•Region/radiation
•Severity/Symptoms
•Time
Cardiac glycosides
Digoxin Antiarrhythmic, inotropic agent
Increases cardiac output, slows the heart rate, increases the force of myocardial contraction: digoxin
Uses:
CHF, a-fib, a-flutter
Adverse reaction:
•fatigue, bradycardia, n/v/d, anorexia, bleeding, toxicity- abdominal pain, n/v, visual
disturbances (YELLOW-GREEN HALO.
•Hypokalemia increases toxicity
Nursing implications:
Take apical pulse for one full minute prior to administering digoxin, hold if rate:
< 60 or > 120 in adult
< 90 in infants
< 70 in children
ANTDOTE IS DIGIBIND
Check serum digoxin (therapeutic level 0.5 to 2.0 ng/nl)
Monitor electrolyte levels to monitor risk for toxicity
ANTICOAGULANTS
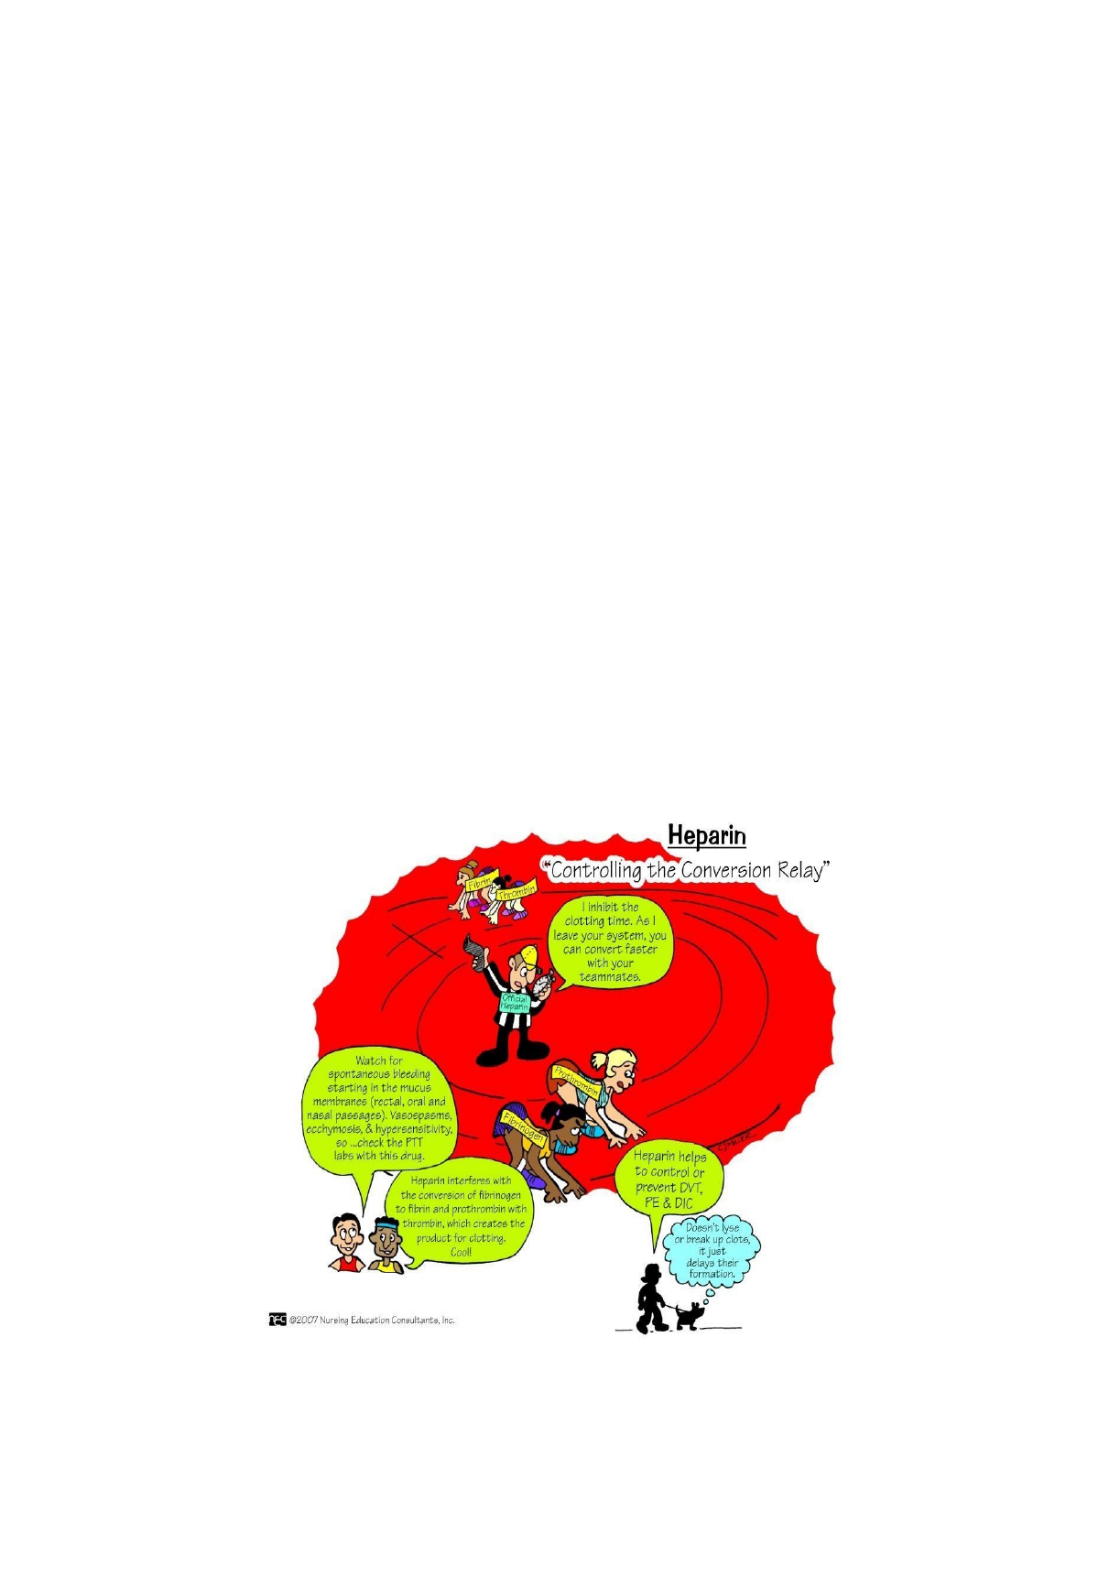
Heparin:
prevents further coagulation from occurring: heparin,
Antidote is protamine sulfate
•Adverse reaction-hemorrhage, bruising, HEPARINE-INDUCED THROMBOCYTOPENIA, hair
loss, osteoporosis, allergic reactions
Nursing implications
•monitor PTT-therapeutic range is 1.5 to 2.5 seconds
•Administer deep Subcutaneously (never IM),
•never message or aspirate,
•monitor for hematuria, black or tarry stools, hematemesis, bleeding gums, blood sputum; report
immediately, stool for OB, no razors, no IMs, use IV control pump, do not d/c abruptly, avoid- ASA,
antihistamines, guaifenesin
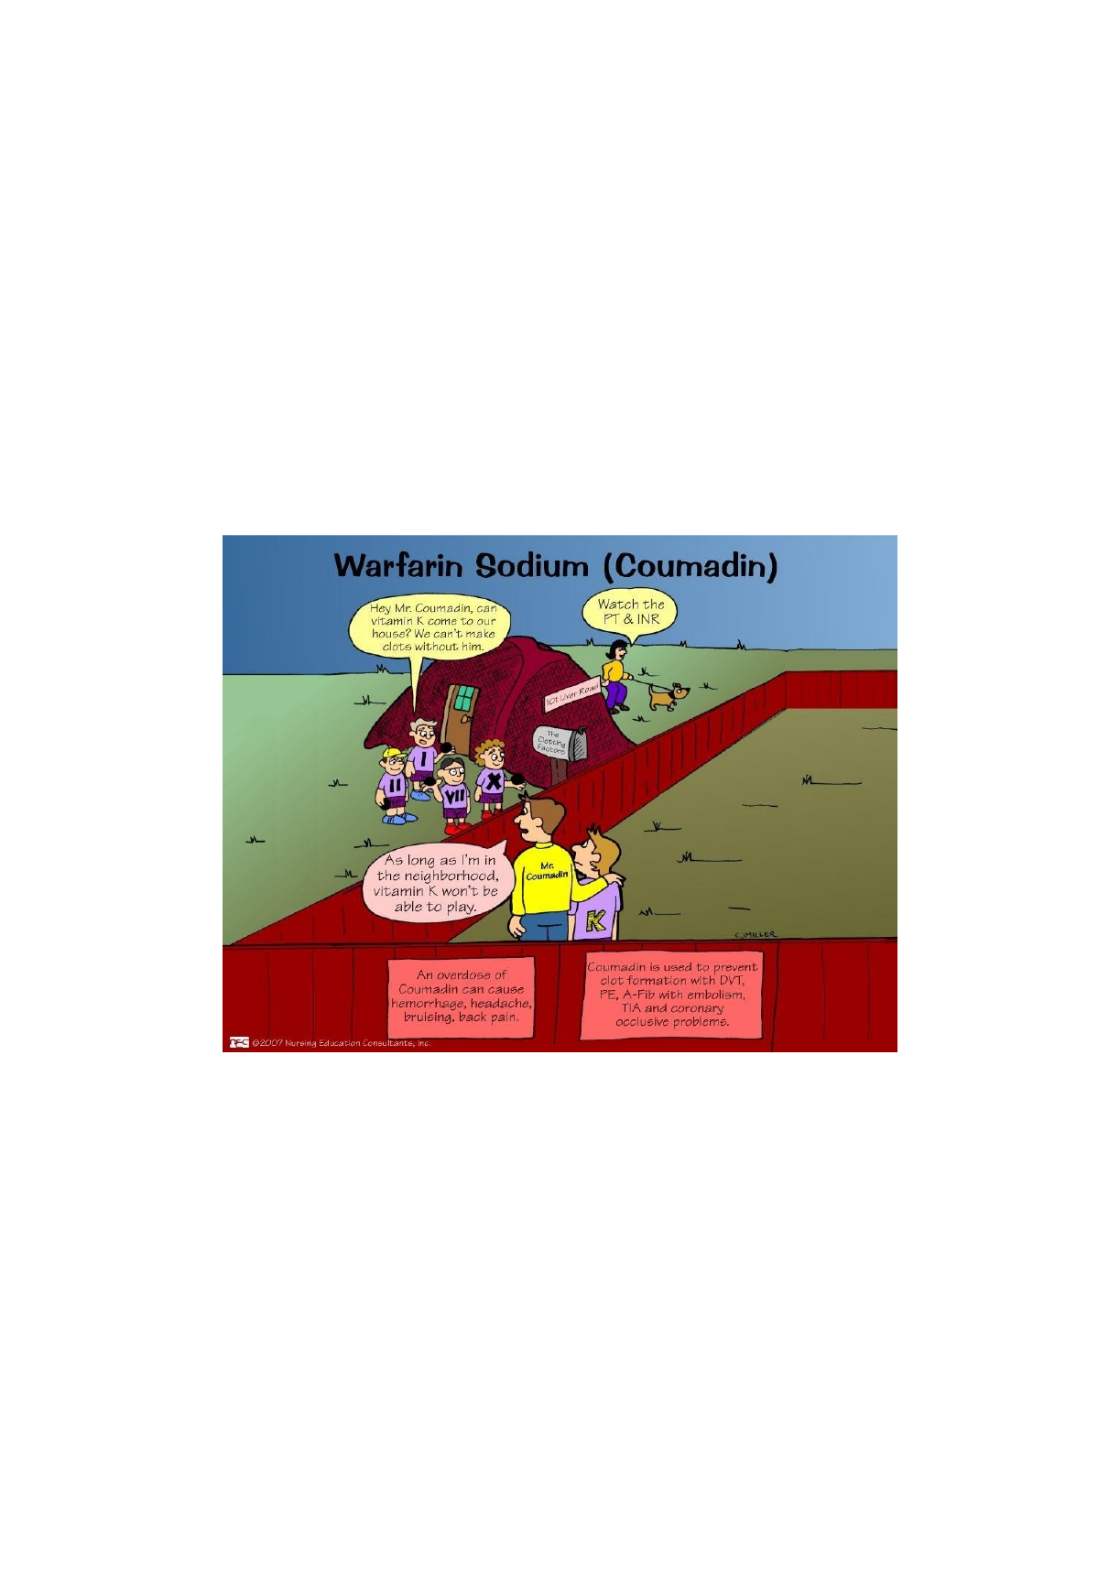
Warfarin
•Uses- venous thrombosis, atrial fibrillation, adjunct therapy of coronary occlusion
Adverse reaction:
•Hemorrhage, nausea, vomiting, anorexia, dermatitis, urticaria, orange-red discoloration of urine,
oversees: paralytic ileus, purple toes syndrome
Nursing implications
⮞ ANTIDOTE IS VITAMIN K
⮞ Monitor PT and INR. PT therapeutic range should be 1 ½ to 2 ½ times the normal value
⮞ Use contraception (fetal damage, demise)
⮞ Report unusual bleeding
⮞ Smoking increases dose requirement
⮞ Use soft toothbrush, floss with waxed floss, use an electric shaver
Lipid lowering agents
Statins
atorvastatin, simvastatin
Prevent metabolism of cholesterol in the body,
Inhibit HMG Coa reductase thus reducing blood lipids.
Adverse reaction:
Statins: contraindicated in pregnancy, hepatotoxic, rhabdomyolysis
Nursing implications-.
⮞ Liver function studies
⮞ Statins should be given at bed time
⮞ Take with food, oral vitamin K may be given prophylactically
Respiratory Drugs
Antiasthmatic
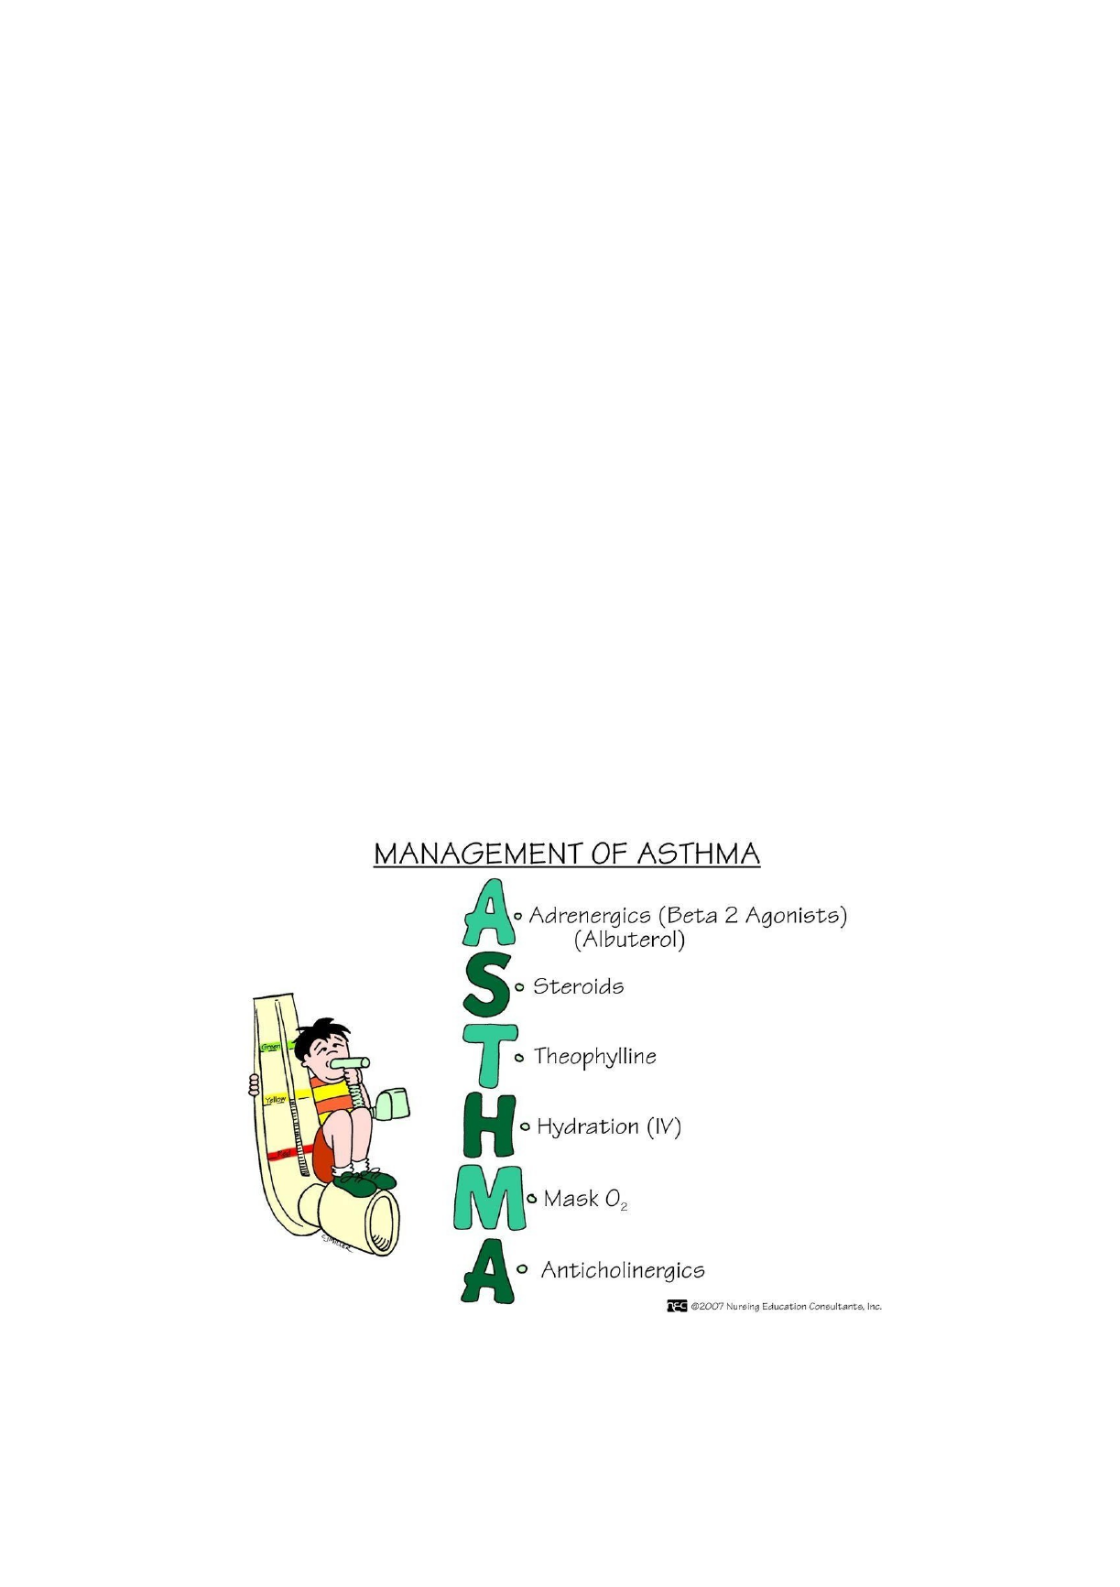
methylxanthine-bronchodilator:Theophilline, Aminophilline, Theodor, Quibron
relaxes bronchial smooth muscle; increases renal blood flow and acts as CNS stimulant.
Uses-emphysema, asthma, CHF
Adverse reaction:
•CNS stimulation; irritability, nervousness, tachycardia, hypotension, GI distress

Nursing implications:
monitor theophilline levels: therapeutic level 10-20 mcg/ml.
⮞
Assess for s & s of toxicity, n/v/d, restlessness, convulsions, and
irregular heart beat.
⮞
Give 1-2 hours before meals or with meals if GI distress.
⮞
Take time-released meds on an empty stomach.
⮞
Avoid excessive caffeine, have diazepam on hand to treat seizures,
avoid smoking.
Mast cell stabilizer
Acts on lung mucosa to prevent histamine release. Cromolyn sodium (Intal), Nedocromil
sodium (Tilade)
Uses: Prophylactically to decrease asthmatic attack, Not to be used in acute asthmatic attacks.
Adverse reaction: bronchoconstriction, cough, rash, dizziness, drowsiness.
Nursing implications
•teach patient use of inhaler: place capsule in container and exhale fully, place mouth piece
between lips tilts head back, inhale deeply and rapidly causing the propeller to spin, remove the
inhaler, hold breath a few seconds and exhale slowly,
•capsules should not be swallowed or open, taper drug if withdrawal is desired.
Antihistamines
Chlorpheniramine maleate, diphenhydramine HCL, Promethazine HCL.
decrease histamine activity by blocking histamine 1receptor sites.
Adverse reaction:
•sedation, anticholinergic side effects (dry mouth, eyes), Paradoxically excitation in children,
dizziness, confusion, decreased BP in elderly.
Nursing implications
•avoid alcohol or other CNS depressants, give with food to decrease GI upset, assess respiratory
function, may thicken bronchial secretions, photosensitivity, reduce dosage of barbiturates given
concurrently with promethazine.
Mucolytics
Acetylcysteine (Mucinex)
decreases viscosity of mucus in bronchial tree.
Uses:

•Cystic fibrosis, pneumonia, emphysema.
Adverse reaction:
•bronchospasm in patient with asthma
Nursing implications:
•have suction equipment readily available; as use of mucolytic, markedly produces copious
secretions,
•Suctioning removes secretions and prevents aspiration, rinse mouth after treatment.
•Incompatible drugs: tetracycline, amphotericin B
ANTIDOTE FOR TYLENOL OVERDOSE
Gastrointestinal drugs
Histamine Antagonists (H2)
Cimetidine, Famotidine, Ranitidine, Naztidine
inhibit the action of histamine at the histamine receptor sites of the stomach, decreasing gastric acid
secretions, allowing healing of ulcerated areas.
Adverse reaction:
•Gynecomastia, prolonged QT interval, confusion, bleeding, hepatotocicity
Nursing implications:
•give antacid one hour before or after administration.
•Therapy may continue for 4-6 weeks or longer.
•Smoking decreases effectiveness.
•Caution: assess for CNS changes in elderly, confusion is a major toxic effect
PPI
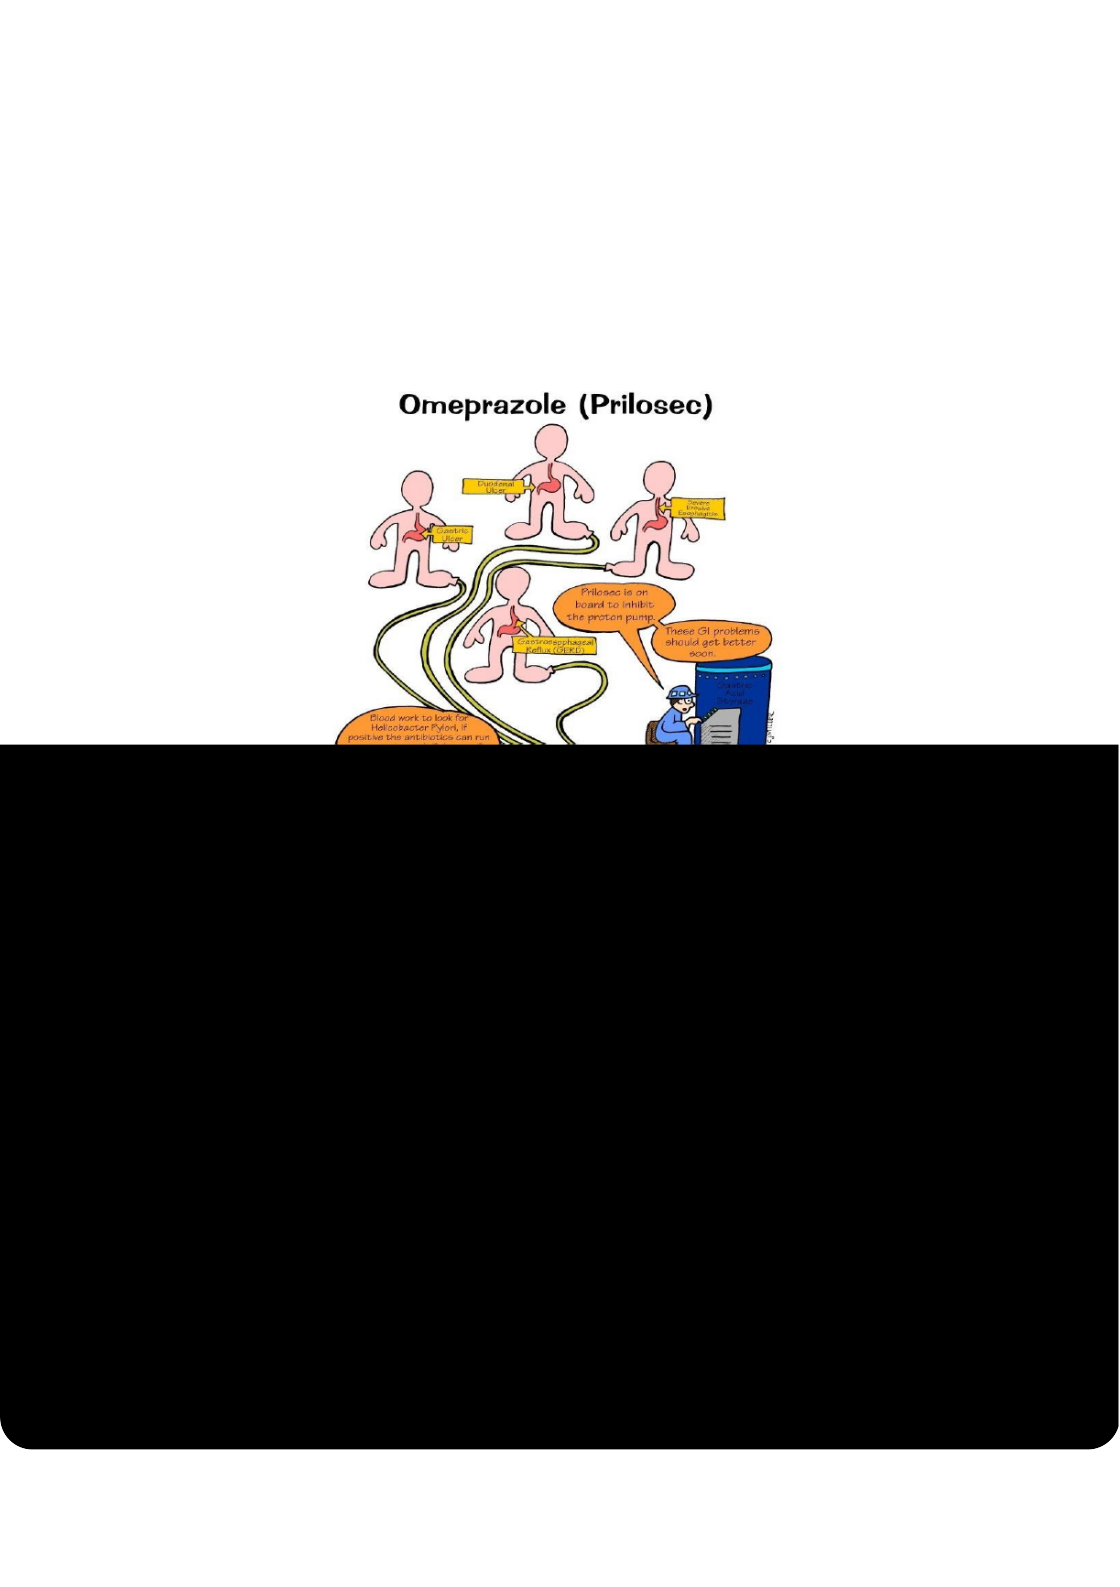
Omeprazole
decreases gastic acid concentration.
Uses: peptic ulcer, gastric esophogeal reflux
Adverse reaction- dizziness, drowsiness, fatigue, headache, chest pain, abdominal pain,
itching, rash.
Nursing implications- can be given with antacids, take drug before meals, swallow capsules
whole, do Not chew or open capsule, avoid driving.
Antacids
•Magnesium antacids neutralize or reduce gastric acidity, increasing pH of the stomach, inhibiting
pepsin. MOM
•Aluminum antacids- binds with phosphate ions in the intestine for form insoluble aluminum
phosphate complexes. Aluminum Hydroxide.
•Sodium carbonate- baking soda
•Calcium carbonate (tums)
•Aluminum magnesium combinations- Magaldrate, Maalox, Gelusil
Uses:
•control ulcer pain, treatmetn of peptic ulcer and esophogeal reflux, prophylaxis for curling’s ulcer
Adverse reaction
Magnesium- contraindicated in client with renal failure, doses . 1.5 ml may have laxative effect,
hypermagnesemia

Aluminum- constipation, accumulation of aluminum in serum, bone and CNS
Sodium carbonate- constipation, sodium retention
Sodium bicarbonate- systemic alkalosis, bloating
Calcium carbonate- hypercalcemia, constipation, alkali syndrome
Aluminum Magnesium combination- constipation or diarrhea, hypermagnesemia
Nursing implications:
•shake liquid antacids before use, tablets must be chewed completely before swallowing,
•take antacid with only small amount of water to prevent diluting the anacid, do not take other oral
drugs within 2 hours of antacid, change in gastric pH may interfere with absorption
•Aluminum: assess elderly for fecal impaction oand intestinal obstruction, assess for s & s of CNS
toxicity, monitor serum phosphorus for hypophosphatemia
•Sodium bicarbonate- assess for milk alkali syndrome, headache, nausea, vomiting, hypercalcemia,
hypophosphatemia
•Calcium carbonate- do not give with milk or foods high in Vitamin D, give 1 and 3 hours after meal
and hs
Antidiarrheals
•Adsorbent: remove irritants form intestine forming protective coating over the mucosa- Bismuth
subsalicylate (PeptoBismol)
•Opiate: slow intestinal motility- Loperamide Hydrochloride (immodium), dephenoxylate
hydrochloride (lomitil)

Adverse reactions
⮞ Adsorbent-darkening of stool, impaction in infants, salicylate toxicity; ringing in ears, rapid
respirations
⮞ Opiate: toxic megacolon in patient with ulcerative colitis, abdominal pain distention,
constipation, dizziness, drowsiness, urinary retention, dry mouth, palpitations, flushing.
Nursing implications
⮞ Adsorbent- use cautiously with aspirin or aspirin containing drugs, serious over dosage can
occur
⮞ Opiate- Imodium should not be taken concurrently with other CNS depressants, have
narcotic antagonist (Naloxone) readily available in case of overdose, withhold in sever
dehydration or electrolyte imbalance
Antiemetics
•Phenothizines - act on vomiting center to relieve nausea and vomiting: Prochlorperazine,
Promethazine
•Antihistamines - block action of acetylcholine in the brain; decrease nausea and vomiting:
Dimenhydrinate (Dramamine), hydroxyzine (Vistaril), Meclizine (Antivert), given for motion
sickness

•Metoclopromide - blocks dopamine receptors in the brain, alleviating nausea and vomiting:
Reglan
Adverse reaction
⮞ Phenothiazines- orthostatic hypotension, EPS, NMS, constipation, dry mouth
⮞ Antihistamines- anticholinergic side effects, CNS: drowsiness, confusion, dizziness
⮞ Metoclopromide
⮞ Drowsiness, restlessness, EPS
Nursing implications
⮞ Phenothiazines
⮞ Avoid driving, sun, maintain fluid intake, report dark urine-expect pink or reddish/brown
urine
⮞ Antihistamines
⮞ Take drug before motion sickness occurs, refrain from driving, avoid alcohol; serious
sedation may occur
⮞ Metoclopromide- report involuntary movement of face, eyes, or limbs, avoid operating heavy
machinery.
Antipeptic Agents
Carafate, SUCRALFATE
promote ulcer healing by forming a protective barrier at the ulcer site.
Adverse reaction- diarrhea and constipation, rash
Nursing implications-
•take drug 1 hour before meals or 2 hours after meal, and at bedtime. Drug more active in
low pH of an empty stomach, administer antacids between doses of sucralfate, but nor with
in ½ hour before or after sucralfate
Antidiabetic Agents
•Insulin
•Transports glucose across cell membranes
•Stimulates synthesis of glycogen form glucose, fats form lipids and protein from amino acids
•May be rapid-acting (regular insulin), intermediate-acting (NPH), Lente) and long acting
(Ultralente).
•Used in the management of IDDM( type I), NIDDM (type II) when not adequatley controlled
by diet and exercise and oral hypoglycemics, DKA or coma, temporary hyperglycemia
related to surgery for infection.

Nursing Considerations: Insulin
⚫Illness, infection, and stress increase the need for insulin insulin should not be withheld at these;
times, because hyperglycemia and ketoacidosis may result.
⚫It is important to know the peak action times of various insulins because of the possibility of
hypoglycemic reactions at these times.
⚫Laboratory evaluation of should be performed .glycosylated hemoglobin (HbA1c) every 3 months
⚫When the client is being kept from eating or drinking for a special procedure, verify with the
physician the need to withhold the morning insulin and determine when food, fluids, and insulin are to
be given.
⚫Instruct the client to always have a spare bottle of insulin available.
⚫Instruct the spouse, significant other, or parents in the administration of intramuscular or
subcutaneous for when the client experiences a hypoglycemic reaction and is unable toglucagon
consume glucose-containing items orally.
Pediatric Considerations
⚫Diluted insulin may be required for some infants to provide small enough doses to avoid
hypoglycemia; diluted insulin should be clearly labeled to avoid dosage errors.
⚫Instruct the child and parents in the age- and development-appropriate administration of insulin.

Nursing Considerations: Complications of Insulin Therapy
Lipoatrophy and Lipohypertrophy
⚫Lipoatrophy, the loss of subcutaneous as a result of repeated insulin injections, appears as slight
dimpling or pitting of subcutaneous fat (see image, top); the use of human insulin helps prevent this
complication.
⚫Lipohypertrophy (see image, bottom), the development of fibrous fatty masses at the injection site, is
caused by the repeated use of an injection site; rotating injection sites will help prevent this
complication.
Dawn Phenomenon
⚫The dawn phenomenon is a result of reduced tissue sensitivity to insulin and, possibly, nocturnal
release of growth hormone, resulting in an increase in the blood glucose level between 5 and 8 AM
⚫Treatment includes an evening dose (or an increase in a current dose) of intermediate-acting insulin
around 10 PM
Somogyi Phenomenon
⚫In the Somogyi effect, a normal or increased blood glucose level is present at bedtime, a decrease to
the hypoglycemic range occurs at 2 to 3 AM, and a subsequent increase occurs as a result of production
of counterregulatory hormones; by 7 AM, hyperglycemia is present.

⚫Treatment includes decreasing the evening (predinner or bedtime) dose of intermediate-acting
insulin or ensuring consumption of an appropriate snack at bedtime.
•Oral hypoglycemic agents
•Can be used only in NIDDM (Type II), lower blood glucose by stimulating endogenous insulin
secretion from beta cells of the pancreas. Intact pancreas function is required.
•Used when diet therapy alone fails to control blood glucose or symptoms or when patients
are not amenable to using insulin
•Contraindications/precautions
•Insulin- contraindicated in hypoglycemia
•infection, stress, or changes in diet may alter requirements, additive hypoglycemic effects
with oral hypoglycemic agents
•Oral hypoglycemic
⮞ Use cautiously in geriatric patients
⮞ Avoid use in patient with severe kidney liver, thyroid and other endocrine
dysfunctions
⮞ Should not be used in pregnancy or lactation
⮞ Alcohol, glucocorticoids, glucagons and thiazide diuretics may decrease
effectiveness
⮞ Use with alcohol may result in disulfiram-like reactions: abdominal cramps,
nausea, headache, flushing, hypoglycemia
•Nursing implications
•Gently roll vial, do not shake vigorously, check expiration date.

•Rotate injection sites regularly and no not inject cold to avoid lipodystophy
•Do not give insulin inaction concentrated IV to avoid sever anaphylactic reactions
•When mixing two types of insulin, draw regular insulin into the first syringe. Use
mixtures within 5-15 minutes of combining them.
•Dosage may change with activity, stress, and diet, check blood glucose levels
frequently
•S/S of hypoglycemia. Advise patient to take a glass of orange juice with 2-3
teaspoons of sugar, honey, or corn syrup dissolved in water, and notify health care
professional, Patient should be advised to carry sugar or a form of glucose and
identification describing medication regime at all times.
•Severe hypoglycemia is treated with glucagon or 50% Dextrose IV.
•Premixed insulin like 70/30 contain 70% NPH and 30% regular insulin and so forth
for 70/25, 50/50.
Pituitary Hormones
Corticotropin- adrenocorticotropin hormone, (ACTH, Acthar)
oAction- stimulates the adrenal cortex to secrete corticosteroids
oUse- diagnostic test for adrenocortical disorders
oNursing Implications- avoid immunizations with live vaccines, diabetics may require an
increased dosage of insulin or oral hypoglycemic
oVasopressin-ADH, Pitressin
Action – hormone secreted by posterior pituitary gland that regulates water
metabolism and prevents dehydration
Use- treatment of DI secondary to ADH deficiency
Side effects-abdominal cramps, angina, myocardial infarctions
Nursing Implications
Monitor B.P. weight and I/O
Drink water with dose to decrease GI distress
Closely monitor patient with history of cardiac disease for s/s or adverse
cardiac effects
Corticosteroids
General Information
Therapeutic effects
•Suppression of inflammation and modification of the normal immune response
•Cortisol replacement in adrenal insufficiency

•Used in autoimmune disease, neoplasms, chronic inflammatory disease,
asthma, allergies, septic shock, cerebral edema and adrenal insufficiency.
Frequently used drugs
•Short acting- cortisone (cortone) and hydrocortisone (solu-cortef)
•Intermediate-acting- prednisone (deltasone), Prednisolone (solu-medrol)
•Long acting- dexamethasone (decadron), Betamethasone (celestone)
Adverse effects
Depression, euphoria, hypertension,
peptic ulceration with long term use,
anorexia, nausea, vomiting, acne,
decreased wound healing, ecchymoses, fragility, hirsutism, petechiae, adrenal
suppression, thromboembolism,
muscle wasting, osteoporosis,
cushingoid appearance, hypokalemia, hyperglycemia, hypocalcemia, chronic use in
children will cause decreased growth
Nursing implications
Observe for mental changes, monitor v/s, weight, I/O, blood glucose level and serum potassium
Assess for and teach patient/family the s/s of adrenal insufficiency/suppression: nausea,
vomiting, anorexia, weakness, weight loss, hypotension, lethargy, restlessness, and confusion.

This is a life threatening complication. Inform patient/family that this may result from abrupt
withdrawal from steroid therapy
Administer in the am as this coincides with natural secretion.
Give po doses with meals because of risk of severe GI irritation and ulcers
Long term therapy requires a diet high in proteins, Ca, K and low in Na and Carbohydrates
Immunosuppression requires patient to avoid crowded places an persons who are ill and to
report any s/s to the physicians immediately. No vaccinations
Counseling for body image
Carry medical alert card or wear bracelet
Topical use: do not use an occlusive dressing; apply only a small amount of ointment
Rinse mouth after using inhaled steroids
Restrict alcohol and caffeine, which further increases GI distress
Thyroids Agents
Thyroid hormones- levothyroxine, (synthroid), liothyronine sodium (cytomel)
Indicated for replacement or substitution therapy in diminished or absent thyroid function, with
restoration of normal hormonal balance
Used in treatment of some types of thyroid cancers
Principal effect is increasing metabolic rate of body tissues
oIncrease utilization of glycogen stores
oStimulate protein synthesis
oPromote cell growth and differentiation
Antithyroid agent- propylthiourcil (PTU)
oInhibits the synthesis of thyroid hormone
oUsed for palliative treatment of hyperthyroidism
oUsed in preparation for thyroidectomy or radioactive iodine therapy
Adverse effects
oThyroid hormone- headache, irritability, insomnia, nervousness, cardiovascular collapse,
arrhythmias, tachycardia, weight loss
oAntithyroid- nausea, vomiting, rash, agranulocytosis, thrombocytopenia

Nursing implications
Thyroid hormones
–Assess apical pulse, B.P, tachyarrhythmias and chest pain prior to an periodically during
therapy
–Labs: thyroid function studies, blood and urine glucose, in diabetic patients- insulin or oral
hypoglycemic dose may need to be increased
–Take medication exactly as directed at the same time each day
–Teach patient to check pulse and notify professional if any adverse effect occurs
–Advise patient to carry identification with medical history, and not to take other medication
without consulting health care professional
Antithyroid agents
oMonitor for improvement of hyperthyroidism symptoms
oAssess for development of hypothyroidism, dosage adjustment may be required
oAssess for skin rash or swelling. Of cervical lymph nodes. Treatment maybe be
discontinued if this occurs.
oLabs: thyroid function studies prior to and periodically during course of therapy
oWBC and differential prior and periodically during course of therapy to monitor for
development of agranulocytosis
oInstruct patient to take medication around the clock, if dose is missed, take as soon as
remembered; take both doses if alomost time for next dose, Consult health professional
if more than 1 dose missed.

Diuretics
oCarry identification with medical history, and not to take other medication without
consulting health care professional
Loop- furosemide (lasix), bumetamide (bumex), prevents reabsorption of sodium and chloride form the
loop of henle and distal renal tubule, increased renal excretion of water and sodium, choloride,
magnesium, hydrogen, and calcium
•Uses- diuresis and subsequent mobilization of excess fluid, (edema and pleural effusion);
lowering of blood pressure.
•Adverse effects – dehydration, hypochloremia, hypokalemia, hyponatremia, hypomagnesium,
hypovolemia, metabolic alkalosis. Hearing loss and tinnitus

Loop
•Nursing interventions
•Assess fluid status throughout therpy
•Monitor vital signs, daily weights, I & O, presence of edema, lung sounds, skin turgor,
and mucus membranes
•Report thirst, dry mouth, lethargy, weakness, hypotension, or oliguria.
•Monitor patient on digitalis, increased risk of digitalis toxicity when taking diuretic
•Monitor labs for electrolyte disturbances
•Assess for hearing problems
Potassium sparing agents - spirolactone (aldactone), triamterene (Dyrenium).
•Causes loss of sodium bicarbonate and calcium while saving potassium and hydrogen ions,
weak diuretic and antihypertensive response when compared to other diuretics.

•Uses- counteracts potassium loss basued by toher agents (thiazides), commonly used with
thiazides, commonly used with thiazides to treat edema or hypotension, treatment of
hyperaldosteronism (spirolactone only)
•Adverse effects – hyperkalemia, hyponatremia, headache, clumsiness, dizziness, constipation, GI
irritation, impotence, bluish urine, use cautiously in geriatric, debilitated and diabetic patients,
patients with renal insufficiency or hepatic dysfunction.
•Nursing interventions- monitor vital signs, daily weights, I & O and B. P. (if used as adjunct for
antihypertensive therapy throughout therapy), labs: electrolytes, BUN, serum creatinine
throughout therapy, caution patients to avoid salt substitutes and food with high levels of
potassium or sodium. May cause dizziness, so advise patient to void driving.
Osmotic diuretics - Mannitol (Osmotrol, Resectisol).
•Increases osmotic pressure of glomerular filtrate thereby inhibiting reabsorption of water and
electrolytes.
•Uses- adjunct therapy in treatment of acute oliguric renal failure, edema, increased intracranial
or intraocular pressure, toxic overdose. Also used as a GU irrigant during transurethal
procedures (2.5 to 5% solution only).
•Adverse effects- headache, confusion, transient volume expansion, CHF, dehydration, sodium
depletion
Nursing Implications

•Monitor vitals, urine output, CVP, and pulmonary artery pressures (PAP) prior to and
through out administration
•Assess patient for s & s of dehydration electrolyte imbalances
•Increased intracranial pressure (ICCP): monitor neurological status and ICCP reading in
patient receiving medication to decrease cerebral edema
•Increased intra-occular pressure: monitor for persistent or increased eye pain or
decreased visual acuity
•Labs: renal function and serum electrolytes
•If crystals are visible in Mannitol solution, warm solution to dissolve them before
administering.
Antiglaucoma agents - acetazolamide (diamox), Methazolamide (Meptazane).
•Inhibits carbonic anhydrase in the eye which resulting in decreased secretion of aqueous humor
thereby lowering intraocular pressure. Also alkaline diuresis preventing uric acid and renal
calculi
•Uses- treatment of intraoccular pressure in glaucoma, control of some types of seizures,
prevention and treatment of acute altitude sickness, prevention of uric and renal calculi
•Adverse effects- depression tiredness, weakness, anorexia, metallic taste, hyperchloremic
acidosis, weight loss, pareshtisias
Nursing interventions
•Observe for sign of hypokalemia
•Monitor response to therapies based on reason for patient receiving medication (ICCP,
glaucoma, altitude, sickness, seizures, etc.)
•Labs: electrolytes, CBC, platelets

Immunosuppressants
General information
Frequently used drug- Azathioprine (Imuran), Cyclophamide (Cytoxan), Methotrexate
(Rheumatrex)
Therapeutic effects
oUsed with gluccocorticoids in the prevention of transplantation rejection reactions
oAlso used in the management of selected autoimmune diseases such as nephritic
syndrome of childhood and sever rheumatoid arthritis.
Adverse effects- use cautiously in patient with infections
Nursing implications and patient teaching
Reinforce need for lifelong therapy to prevent transplant rejection
Monitor for infection
Assess for s & s of organ rejection
Protect patients on immunosuppressants from staff and visitors who carry infections.
Advise patietn to avoid contact with contagious persons.
Arthritis Drugs
Gold compound (Auronofin (Riduaura)
oTherapeutic effects
oUsed for treatment of progressive rheumatoid arthritis resistant to conventional therapy by
inhibiting inflammatory process
oModify immune response and slows disease process of rheumatoid arthritis
oProvides relief of pain and inflammation
Adverse effects- dizziness, headache, syncope, abdominal pain, cramping, diarrhea, metallic
taste, stomatitis, dermatitis, rash, agranulocytosis, aplastic anemia, anemia, thrombocytopenia,
allergic reactions icluding anaphylaxis
Nursing implications and patient teaching
oAssess patient’s range of motion and degree of swelling and pain in affected joints.
oMonitor patient nitroid reaction (flushing, fainting, dizziness, vomiting, etc…) that may occur
immediately to 10 minutes following IM injection.
oMonitor renal, hepatic, and hematological function and urinalysis
oConcurrent therapy with other anti-inflammatories is usually necessary

Antigout Agents
Allopurinol (Zyloprim), Colchicine (Novocolchine), Probenicid (Benebid)
oTherapeutic effects
Used for treatment of active gout (colchicines) and prevention of recurrent attacks
Reduce the inflammatory response or lower uric acid by either enhancing its renal
excretion or decreasing its production
Inhibits the production of uric acid thereby lowering the serum levels
oAdverse effects- drowsiness, diarrhea, hepatitis, nausea, vomiting, rash, uticaria, bone
marrow depression
oNursing implications and patient teaching
Assess patient’s joint pain and swelling, assess for rash or more sever
hypersensitivity reactions, monitor uric acid levels, administer with or after meals,
may occasionally cause drowsiness so avoid driving, monitor I & O
Antipyretics
Acetaminophen (Tylenol), Aspirin (ASA), Ibuprofen (Advil), Naproxen (Naprosyn)
oTherapeutic effects- used for lower fever of many causes, antipyretics lower fever by
affecting thermoregulation in the CNS, aspirin has the most profound effect on the
platelet function
oAdverse effects- aspirin, ibuprofen naproxen are all contraindicated in bleeding
disorders. Use cautiously in patients with ulcer disease, chronic use of acetaminophen
may lead to hepatoxicity and interfere with digitalis, centers for disease control and
prevention warns against giving aspirin to children or adolescents with varicella or
influenza-like or viral illnesses because of possible association with Reye’s syndrome.
Nursing implications and patient teaching
oAssess fever, note presence of associated symptoms
oAdminister with food or antacids to minimize GI irritation
oAdvise patient to consult health care professional if fever is not relived by routine doses
or if fever is greater than 103 F or 39.5 C
oMonitor s & s of salicylism: tinnitus, confusion, dizziness, nausea and vomiting
NSAIDS
NSAIDS: Aspirin (ASA), fenoprofen (Nalfon), Ibuprofen (Advil), Indomethacin (Indocin), Naproxen,
(naprosyn)
Nonopioid analgesics: acetaminophen (Tylenol), fenoprofen, ibuprofen, ketoprofen, naproxen,
phenazopyridine (Phenazadine)
Therapuetic effects

•Used for mild to moderate pain, fever and various inflammatory conditions such as
rheumatoid arthritis and osteoarthritis
•Acetaminophen has analgesic and antipyretic effect, but is not effective as an anti-
inflammatory agent
•Phenazopyridine is used as a urinary tract analgesic only
Adverse effects
•Hypersensitivity to aspirin is a contraindication for the whole class of NSAIDS
•Only acetaminophen is sage for occasional use in pregnancy and lactation
•Use cautiously in patients with history of bleeding disorders, GI bleeding or
severe hepatic, renal or cardiovascular disease
•Patients with asthma, aspirin-induced allergy and nasal polyps are at risk for
hypersensitive reactions.
Nursing Implications
•Assess drugs taken, for short-term use, combined doses of acetaminophen and
salicylates should not exceed the recommended dose of either drug given alone.
•Arthritis: assess pain and ROM 1-2 hours after dose, Pain assess pain before and
after drug administration.
•Labs: monitor bleeding time
•Advise patient to take drug with full glass of water and remain in upright
position for 15-30 minutes afterward

•Caution patient to avoid concurrent use of alcohol, aspirin, acetaminophen or
other OTC drugs without consulting a health care professional
Opioid Analgesics
Codeine, morphine, meperidine (demerol), hydromorphone (dilaudid), oxcycodone (oxycontin),
ocycodone/acetaminophen (percoet), fentanyl (duragesic)
Therapeutic effect
•Used for control moderate to severe pain
•Some use as general anethetic adjuncts
Side effects: sedation, confusion, euphoria, hypotension, n/v, severe constipation,
respiratory depression, chronic use may result intolerance and the need for larger doses
to relieve pain; psychological or physical dependence may occur, abrupt discontinuation
if physical dependence is present may result in withdrawal symptoms.
Nursing implications and patietn teaching
•Assess type, location, and intensity of pain prior to and at peak following
administration
•Monirtorvital signs before and after administration, especially respirator
assessment
•Assess pain regularly, using pain scale, and administer pain medication
accordingly, regularly scheduled medication regimen result in more effective
pain management than pm administration that is, waiting or patient to request
medication.
•NARCAN IS THE ANTIDOTE FOR NARCOTIC OVERDOSE
•Advise patient to increase fluid intake, eat foods high in fiber, and take stool
softener is prescribed

Anticholinergics
Frequently used drugs: Atropine, scopolamine, glycopyrrolate
Therapeutic effects
•Blocks the effects of acetylcholine and inhibits parasympathetic actions
•Used preoperatively to decrease respiratory tract secretions
•Atropine is first line drug used for symptomatic bradycardia
•Reduction of tremor or rigidity in Parkinsonism
•Eye drops used for eye exams to produce mydriasis
•Antidote for use of parasympathetic drugs.
Adverse effects
Dizziness, confusion, dry mouth, dry eyes, blurred vision, constipation, paralytic ileus, geriatric
and pediatric patients are more susceptible to adverse effects

Contraindicated in patients with narrow-angle glaucoma, sever hemorrhage, tachycardia due to
thyrotoxicosis or cardiac insufficiency) or myathenia gravis
Nursing implications and patient teaching
oVitals and ECG frequently during IV drug therapy
oPromptly report any significant change in hear rate or BP, increase in ventricular ectopy,
or angina
oMonitor I & O ratios in elderly or surgical patients; may cause urinary retention
oAssess patient regularly or surgical patients, may cause urinary retention
oAssess patient regularly for abdominal distention, auscultate for bowel sounds,
constipation may become a problem. Increasing fluids and adding build to diet may help
alleviate constipation.
oInstruct patietn that frequent rinses, sugarless gum or candy, and food oral hygiene may
help relieve dry mouth.
oMay cause drowsiness, caution patient to avoid driving
oOphthalmic: advise patietn that eye preparations may temporarily blur vision and impair
ability to judge distances; dark glasses may be needed to protect eyes form bright light
Antiparkinsonians
Frequently used drugs-Trihexyphenidyl (Artane), Benztropine (Cogentin), Dopanime agonists:
carbidopa/Levodopa (Sinemet)
Therapeutic effects
•Used in the treatment of parkinsonism of various causes degenerative, toxic,
infective, neoplastic, or drug induced.
•Treatment aimed at restoring natural balance of two major CNS
neurotransmitters: acetylcholine and dopamine
Adverse effects
•Anticholinergics should be avoided in patients with narrow angle glaucoma, use
cautiously in patient with severe cardiac disease, pyloric obstruction or prostatic
enlargement. Drowsiness, dizziness, orthostatic hypotension
Nursing implications and patient teaching
Monitor vitals, assess parkinsonian and EPS
Advise patient that drowsiness or dizziness any occur and to avoid driving
Change position slowly to minimize orthostatic hypotension
Caution patient that decreased perspiration may occur
Overheating may occur during hot weather

Advise patietn to increase activity
Fluids and ass bulk to diet may
Anticonvulsants
General action
oA variety of agents which are capable of depressing abnormal neuronal discharges in the
CNS that may result in seizures.
oAlso prevent the spread of seizure activity by depressing the motor cortex, raising the
seizure threshold, or altering the levels of neurotransmitters, depending on the group
Class Drug Type of Seizure
Barbiturates Phenobarbital (Luminal), Primidone
(Myosline)
Tonic – clonic and partial (focal) seizures
Prophylaxis of partial seizures
Benzodiazepines Clonazepam (Clonopin)
Clorazepate (Tranxene)
Diazepam (Valium)
Lorazepam (Ativan)
Akinteci seizures, Myoclonic
Partial
Status epilepticus, tonic-clonic
Status epilepticus
Hydantoins Foshphenytoin
Phenytoin (Dilantin)
Short term management of seizures,
treatment/prevention of seizures during
neurosurgery
Tonic-clonic and partial with complex
symptomatology
Succinimides Ethosuximide (Zarontin) Absence seizures
Miscellaneous Acetazolamide (Diamox)
Carbamazepine (Tegretol)
Magnesium Sulfate
Tonic-Colonic, complex partial
Eclamptic seizures

Adverse effects
oMental dullness, ataxia, lethargy, drowsiness, headache, nystagmus, diplopia, mental
changes, withdrawal seizures if drug is stopped abruptly, emotional changes including
depression, irritability, impotence, respiratory depression, gastric distress
Nursing Implications and Patient Teaching
oAssess location, duration, and characteristics of seizure activity
oMonitor serum drug levels routinely throughout anticonvulsant therapy especially when
adding or discontinuing agents.
oAdminister drug around the clock, implement seizure precautions, instruct patient to take
medication every day, exactly as directed, caution patient to avoid driving alcohol, advise
patietn to avoid taking alcohol or other CNS depressants
oAdvise patient to carry identification
Sedatives/Hypnotics
Frequently used Drugs
Antihistamins: Diphenhydramine (Benadryl), Hydroxyzine, (Vistaril)
Barbiturates: Pentobarbitol (Nembutal), Phenobarbital (Luminal),
Benzodiazepines: Alprazolam (Xanax), Diazepam (Valium),Midazelam (Versed), Chlordiazepoxide
(Librium)
Miscellanious: Zolpidem (Ambien)
Therapeutic effects: causes generalized CNS depression
oSedatives- used in the treatment of varoius anxiety states and to provide sedation before
procedure
oHypnotics- are used to treat insomnia
oSelected drugs are used as
–Anticonvulsants, skeletal muscle relaxants (Diazepam)
oAdjuncts in the treatment of alcohol withdrawal (chlordiazepoxide)
oAs amnestics and adjunct to general anesthesia
Adverse effects
⮞ May produce tolerance with chronic use
⮞ Have potential for psychological or physical dependence
⮞ Should not be used in patients with uncontrolled severe pain, these agents do not habe
analgesic properties
⮞ Use cautiously in patients with
⮞ Hepatic dysfunction, severe renal impairment or severe underlying pulmonary disease
⮞ Suicidal tendencies or previous history of addiction
⮞ Hypnotic uses should be short term.
Nursing implications and Patient Teaching
Monitor vitals and respiratory status frequently throughout IV administration
Insomnia: assess sleep patterns before and during therapy
Anxiety: assess degree of anxiety and lebel of sedation
Seizures: observe and record intensity, duration and charateristics of seizure activity and
institute seizure precautions
Muscle spasms: assess muscle spasms, associated pain, and limitation of movement before and
throughout therapy
Alcohol withdrawal: assess patient experiencing alcohol withdrawal for tremors, agitation,
delirium, and hallucinations. Protect from injury
Prefix, root,
suffix Examples (generic names) Drug class or drug category
-afil avanafil; sildenafil; tadalafil; vardenafil phosphodiesterase (PDE) inhibitor
-asone
betamethasone; dexamethasone; diflorasone; fluticasone;
mometasone corticosteroid
-bicin doxorubicin; epirubicin; idarubicin; valrubicin antineoplastic; cytotoxic agent
-bital butabarbital; butalbital; phenobarbital; secobarbital barbiturate (sedative)
-caine bupivacaine; lidocaine; mepivacaine; prilocaine; proparacaine local anesthetic

cef-, ceph- cefaclor; cefdinir; cefixime; cefprozil; cephalexin cephalosporin antibiotic
-cillin amoxicillin; ampicillin; dicloxacillin; nafcillin; oxacillin penicillin antibiotic
cort clocortolone; fludrocortisone; hydrocortisone corticosteroid
-cycline demeclocycline; doxycycline; minocycline; tetracycline tetracycline antibiotic
-dazole albendazole; mebendazole; metronidazole; tinidazole anthelmintic; antibiotic; antibacterial
-dipine amlodipine; felodipine; nifedipine; nimodipine; nisoldipine calcium channel blocker
-dronate alendronate; etidronate; ibandronate; risedronate
bisphosphonate; bone resorption
inhibitor
-eprazole esomeprazole; omeprazole; rabeprazole proton pump inhibitor (PPI)
-fenac bromfenac; diclofenac; nepafenac NSAID
-floxacin
besifloxacin; ciprofloxacin; levofloxacin; moxifloxacin;
ofloxacin quinolone antibiotic
-gliptin saxagliptin; sitagliptin; linagliptin
antidiabetic; inhibitor of the DPP-4
enzyme
-glitazone pioglitazone; rosiglitazone; troglitazone antidiabetic; thiazolidinedione
-iramine brompheniramine; chlorpheniramine; pheniramine antihistamine
-lamide acetazolamide; brinzolamide; dorzolamide; methazolamide carbonic anhydrase inhibitor
-mab
adalimumab; daclizumab; infliximab; omalizumab;
trastuzumab monoclonal antibody
-mustine carmustine; estramustine; lomustine; bendamustine alkylating agent (antineoplastic)
-mycin azithromycin; clarithromycin; clindamycin; erythromycin antibiotic; antibacterial
-nacin darifenacin; solifenacin muscarinic antagonist (anticholinergic)
-nazole
fluconazole; ketoconazole; miconazole; terconazole;
tioconazole antifungal
-olol atenolol; metoprolol; nadolol; pindolol; propranolol; timolol beta blocker
-olone fluocinolone; fluorometholone; prednisolone; triamcinolone corticosteroid
-olone nandrolone; oxandrolone; oxymetholone anabolic steroid

-onide budesonide; ciclesonide; desonide; fluocinonide; halcinonide corticosteroid
-oprazole dexlansoprazole; lansoprazole; pantoprazole proton pump inhibitor (PPI)
parin; -parin dalteparin; enoxaparin; fondaparinux; heparin; tinzaparin
antithrombotic; anticoagulant (blood
thinner)
-phylline aminophylline; dyphylline; oxtriphylline; theophylline xanthine derivative (bronchodilator)
-pramine clomipramine; desipramine; imipramine; trimipramine tricyclic antidepressant (TCA)
pred; pred- loteprednol; prednicarbate; prednisolone; prednisone corticosteroid
-pril benazepril; captopril; enalapril; lisinopril; moexipril; ramipril ACE inhibitor
-profen fenoprofen; flurbiprofen; ibuprofen; ketoprofen NSAID
-ridone iloperidone; paliperidone; risperidone atypical antipsychotic
-sartan candesartan; irbesartan; losartan; olmesartan; valsartan angiotensin II receptor antagonist; ARB
-semide furosemide; torsemide loop diuretic (water pill)
-setron
alosetron; dolasetron; granisetron; ondansetron;
palonosetron serotonin 5-HT3 receptor antagonist
-setron dolasetron; granisetron; ondansetron; palonosetron antiemetic and antinauseant
-statin
atorvastatin; lovastatin; pitavastatin; pravastatin;
rosuvastatin; simvastatin HMG-CoA reductase inhibitor; statins
sulfa- sulfacetamide; sulfadiazine; sulfamethoxazole; sulfasalazine
antibiotic; anti-infective; anti-
inflammatory
-tadine cyproheptadine; desloratadine; loratadine; olopatadine antihistamine
-tadine amantadine; rimantadine antiviral; anti-influenza-A
-terol albuterol; arformoterol; formoterol; levalbuterol; salmeterol beta agonist; bronchodilator
-thiazide chlorothiazide; hydrochlorothiazide; methyclothiazide thiazide diuretic (water pill)
-tinib crizotinib; dasatinib; erlotinib; gefitinib; imatinib antineoplastic (kinase inhibitor)
-trel desogestrel; etonogestrel; levonorgestrel; norgestrel female hormone (progestin)
tretin-; tretin; -
tretin acitretin; alitretinoin; isotretinoin; tretinoin
retinoid; dermatologic agent; form of
vitamin A
-tyline amitriptyline; nortriptyline; protriptyline tricyclic antidepressant (TCA)
vir; -vir adefovir; entecavir; ribavirin (along with interferon) antiviral; anti-hepatitis
-vir cidofovir; ganciclovir; valganciclovir antiviral; anti-CMV
-vudine lamivudine; stavudine; telbivudine; zidovudine antiviral; nucleoside analogues
-zodone nefazodone, trazodone, vilazodone antidepressant
-zosin aFDAlfuzosin; doxazosin; prazosin; terazosin alpha blocker
-triptan almotriptan; eletriptan; rizatriptan; sumatriptan;
zolmitriptan
antimigraine; selective 5-HT receptor
agonist
vir; -vir
abacavir; efavirenz; enfuvirtide; nevirapine; ritonavir;
tenofovir antiviral; anti-HIV
-vir acyclovir; famciclovir; penciclovir; valacyclovir antiviral; anti-herpes
-vir oseltamivir; zanamivir antiviral; anti-flu
-zepam clonazepam; diazepam; flurazepam; lorazepam; temazepam benzodiazepine
-zolam alprazolam; estazolam; midazolam; triazolam benzodiazepine
Herbal Medicines
Herb Action and Uses Nursing Considerations
Echinacea- american
cone flower, black
susans coneflower
Action: herb extract stimulates immune system
and reduces growth of bacteria
Uses: wound-healing agent for abscesses,
burns, eczema, leg ulcers, and other skin
wounds. Nonspecific immune stimulant and
anti-infective
Caution in pregnant and breastfeeding women to
avoid her use; effects are unknown
Many tinctures contain significant alcohol and
may not be suitable for children, alcoholic
patients or those with liver disease
Advise patients to inform health care providers
of herbal use if medication is prescribed
Advise patietn that prolonged use (over 8 weeks)
may cause overstimulation of immune system
resulting in immune system suppression.
Garlic Action: may exhibit antithrombotic, lipid
lowering, antimicrobial effects. Uses:
antihypertensive, antimicrobial. Reduces
morbidity in AIDS patients. Prevention of age
related vascular changes
Advise patient if using to lower cholesterol level
to notify health care provider to monitor serum
levels.
Risk of bleeding when used concomitantly with
anticoagulants, antiplatelets and other herbs
Lower serum lipid levels with anticoagulation effects.
Discourage heavy use of garlic before surgery
Instruct patient to watch for bleeding signs
Ginger Action: inhibits platelet aggregation
Uses: antiemetic, motion or sea sickness, pain
and swelling of rheumatoid arthritis
Patient receiving anticoagulant should take
ginger under medical supervision
Monitor patient for bleeding
No more than 6 grams of dried powder ginger
should be taken on an empty stomach
Ginko Action: causes arterial vasodilation increasing
tissue perfusion and cerebral blood flow.
Uses: treatment of cerebrovascular disease,
peripheral vascular insufficiency
Caution patient to avoid herb is on
anticoagulants
Avoid use if history of seizure disorder
Monitor patietn for bleeding or unusual bleeding
Ginseng Action: may exert opposing effects, ie, one has
CNS stimulating effect.
Uses: some decrease fatigue, improve stamina,
and well-being in elderly patients.
Other used as sedatives or sleep aids
When taken in large doses with other stimulants,
paint may exhibit signs of ginseng abuse
syndrome (diarrhea, hypertension, restlessness,
insomnia, skin eruptions, depression, appetite
suppression, euphoria, and edema)
Advise patient not to take herb for prolonged
period.
Advise diabetic patient to check blood glucose
levels closely until effects of herbs are known.
St. John’s wort Action: herb inhibits stress-induced increase in
corticotropin-releasing hormone, corticotropin
and cortisone. Also has antiviral activity,
including effect on retroviruses.
Uses: treat mild to moderate depression,
hypothyroidism, insomnia. Also, HIV infection
topically for skin diseases including Kaposi’s
sarcoma
Depression should be medically evaluated as
conventional therapy may be needed for more
severe disorder.
Advise patietn that herb interacts with many
other drugs and OTC products.
Her had mutagenic effects on sperm cells and
ova, so should not be used by those planning
pregnancy, including men.

