


Wound Healing
The final phase of the inflammatory response is healing. Healing includes the two major
components of regeneration and repair.
•1. Regeneration
•Replacement of lost cells and tissues with cells of the same type
•Ability to regenerate depends on cell type.
•Constantly dividing cells that rapidly regenerate
•Skin, bone marrow, lymphoid organs, as well as mucous membrane cells
of the urinary, reproductive, and GI tracts
•Replacement of lost cells and tissues with cells of the same type
•Stable cells such as liver, bone, kidney, and pancreas regenerate in response to
injury.
•Permanent cells such as neurons and skeletal and cardiac muscle do not divide.
•Neurons are replaced by glial cells or stem cells.
•Skeletal and cardiac muscle will be repaired with scar tissue.
•2. Repair
•Healing as a result of lost cells being replaced with connective tissue
•More common and complex than regeneration
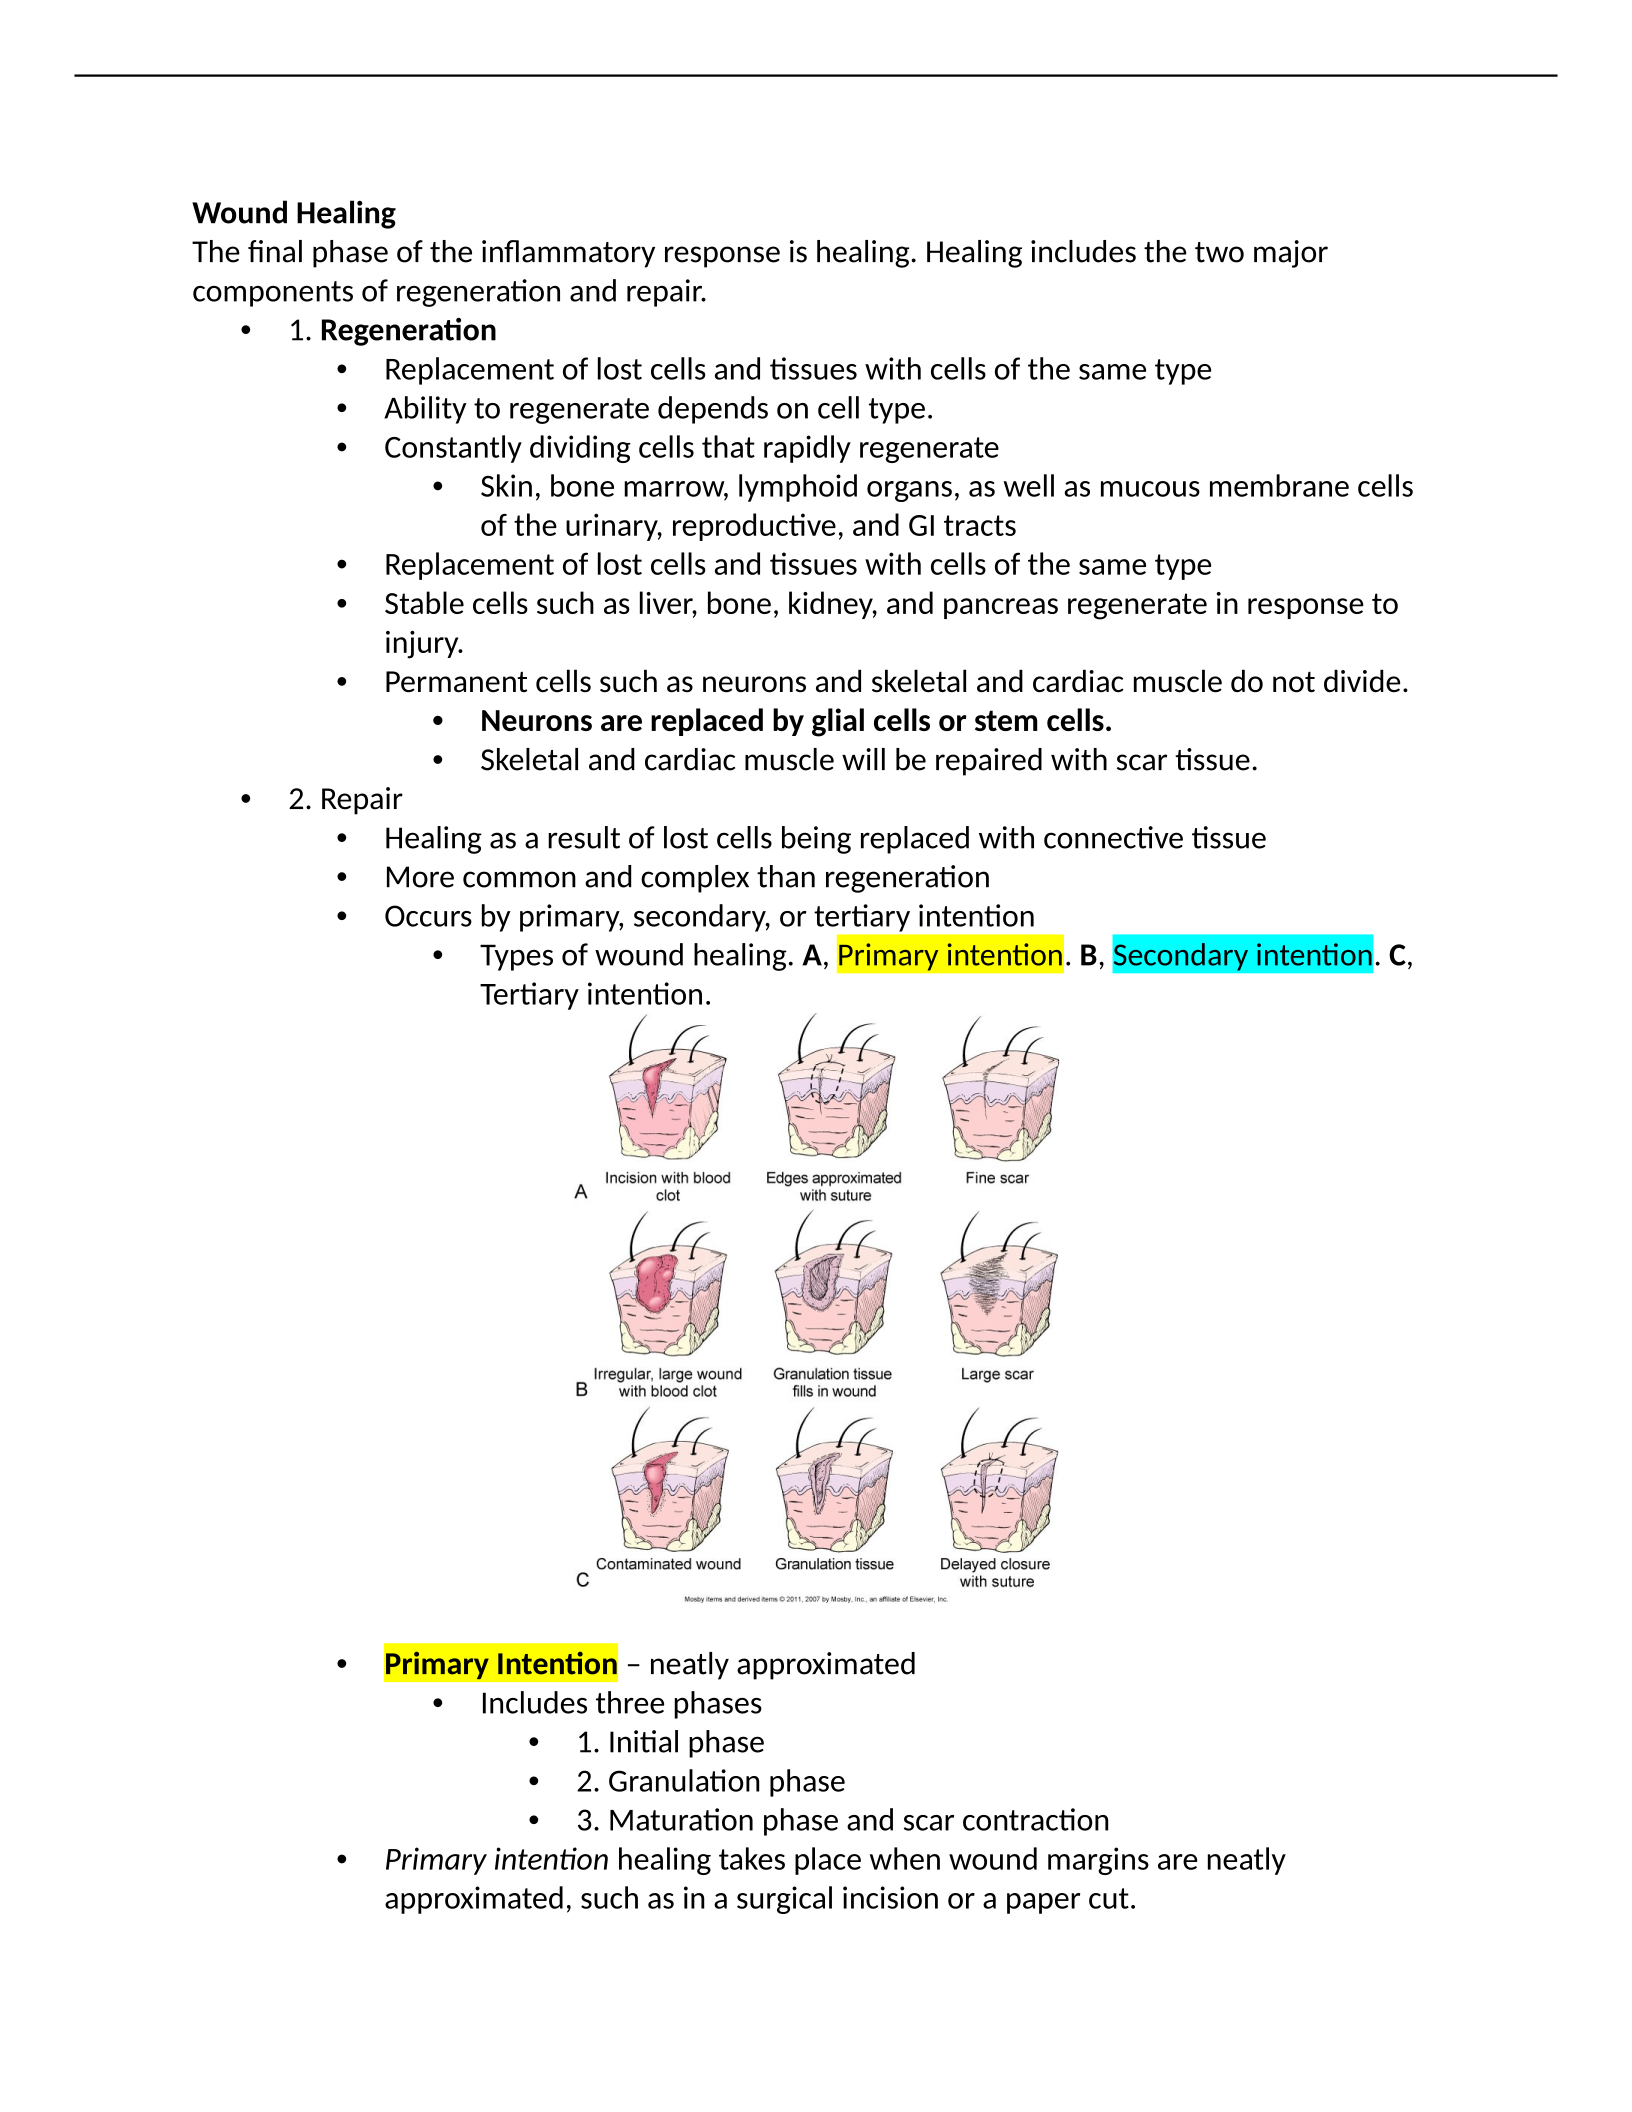
•Occurs by primary, secondary, or tertiary intention
•Types of wound healing. A, Primary intention. B, Secondary intention. C,
Tertiary intention.
•Primary Intention – neatly approximated
•Includes three phases
•1. Initial phase
•2. Granulation phase
•3. Maturation phase and scar contraction
•Primary intention healing takes place when wound margins are neatly
approximated, such as in a surgical incision or a paper cut.
•1. Initial Phase
•Lasts 3 to 5 days
•Edges of incision are aligned.
•Area composed of: fibrin clots, neutrophils, erythrocytes macrophages
ingest wound debris fibrin clot serves as a meshwork for migration of
epithelial cells
•The area of injury is composed of fibrin clots, erythrocytes, neutrophils (both dead and
dying), and other debris. Macrophages ingest and digest cellular debris, fibrin fragments,
and RBCs. Extracellular enzymes derived from macrophages and neutrophils help digest
fibrin. As the wound debris is removed, the fibrin clot serves as a meshwork for future
capillary growth and migration of epithelial cells.
•Repair
•2. Granulation Phase
•Lasts 5 days to 3 weeks
•Fibroblasts migrate to site.
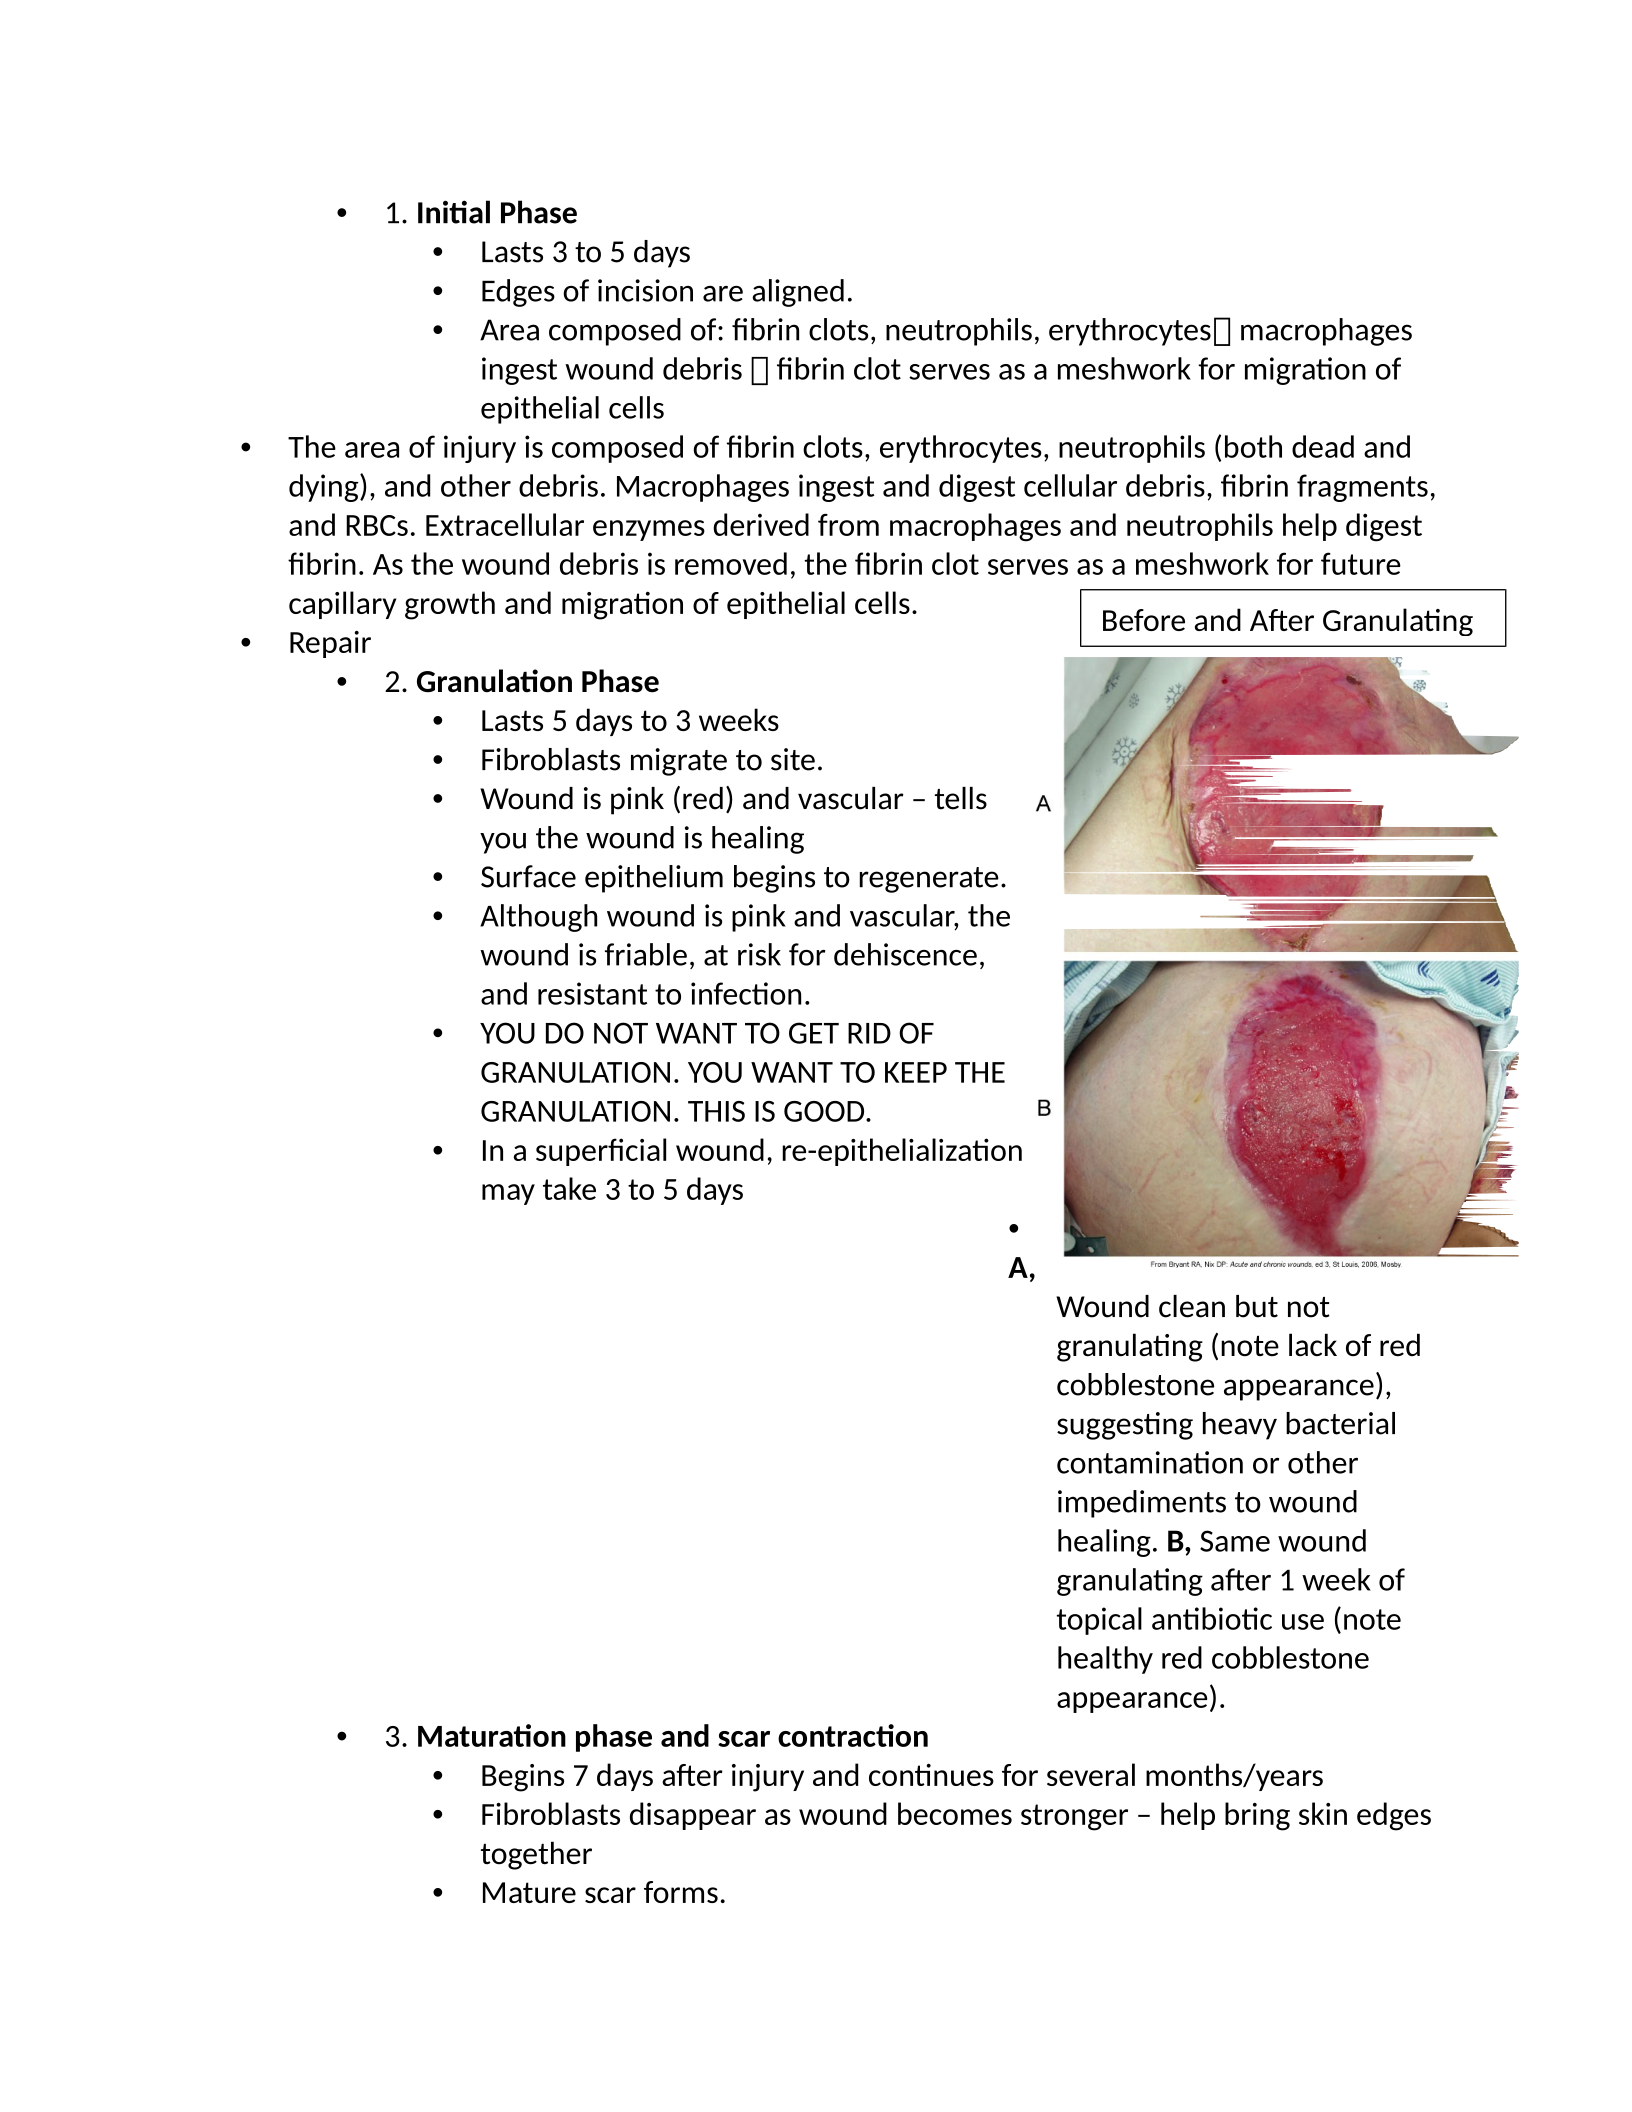
•Wound is pink (red) and vascular – tells
you the wound is healing
•Surface epithelium begins to regenerate.
•Although wound is pink and vascular, the
wound is friable, at risk for dehiscence,
and resistant to infection.
•YOU DO NOT WANT TO GET RID OF
GRANULATION. YOU WANT TO KEEP THE
GRANULATION. THIS IS GOOD.
•In a superficial wound, re-epithelialization
may take 3 to 5 days
•
A,
Wound clean but not
granulating (note lack of red
cobblestone appearance),
suggesting heavy bacterial
contamination or other
impediments to wound
healing. B, Same wound
granulating after 1 week of
topical antibiotic use (note
healthy red cobblestone
appearance).
•3. Maturation phase and scar contraction
•Begins 7 days after injury and continues for several months/years
•Fibroblasts disappear as wound becomes stronger – help bring skin edges
together
•Mature scar forms.
Before and After Granulating

•HENCE, reason abdominal surgery discharge instructions limit lifting for
up to 6 weeks.
•This is the reason abdominal surgery discharge instructions limit
lifting for up to 6 weeks.
•Active movement of the myofibroblasts causes contraction of the healing
area, helping to close the defect and bring the skin edges closer together.
•The scar may be more painful at this phase than in the granulation phase.
•Secondary Intention
•Wounds that occur from trauma, ulceration, and infection have large amounts of
exudate and wide, irregular wound margins with extensive tissue loss.
•Edges cannot be approximated.
•Results in more debris, cells, and exudate
Powered by TCPDF (www.tcpdf.org)

