


ASSESSMENT OF FACTORS INFLUENCING SERVICE DELIVERY AT SUB-
COUNTY HOSPITALS IN MERU COUNTY, KENYA

1
CHAPTER ONE
INTRODUCTION
1.1 Background of the Study
Integrated and people-centred health services are critical for realizing universal health care
coverage. This can only be achieved through provision of efficient and effective health services.
Service delivery is one of the key building blocks of any health system, it is an immediate output
of the inputs into the health system, such as the health workforce, procurement and supplies,
infrastructure and financing. Adequate provision of inputs should lead to enhanced service
delivery and access to services.
Ensuring availability of health services that meet a minimum quality standard and securing
access to them are key functions of a health system. According to World health organisation
[WHO] (2007), good health services are those which deliver effective, safe, quality personal and
non-personal health interventions to those who need them, when and where needed, with
minimum waste of resources.
Services is a process consisting of a series of more or less intangible activities that normally, but
not necessarily always, take place in interactions between the customer and service employee
and/or physical resources or goods and/or systems of the service provider, which are provided as
solutions to customer problems (Grönroos, 2011). Moreover, service is seen as any act or
performance one party can offer to another that is essentially intangible and does not result in the
ownership of anything (Kotler, 2008).
Service delivery as a series of highly localized actions by agents in public agencies or private
enterprises to provide needed goods and services to citizen beneficiaries in a way that meets their
expectations. Service delivery has a life-cycle span (i.e plan, design, operate, maintain, and

2
monitor) to sustain services such as nutrition or transport or goods such as electricity or water to
citizen beneficiaries (Lockwood & Smits, 2011). Getting (or Delivering) these services or
goods requires access by citizen beneficiaries, and the goods or services should meet the
expectations of the beneficiaries, which implies taking into account their needs and demands
(Fiszbein et al., 2011).
WHO (2010), states that patients’ service delivery includes provision of health services at all
levels as per the standard which include speed of delivery, harmonization at service delivery
point, effectiveness of the services, patient safety, ethics and professionalism in during provision
of service. To better understand the degree of service delivery, there is need to understand
customer satisfaction because the level of service delivery and quality of service are mainly
related to customer satisfaction. Customer satisfaction is a person’s feeling of pleasure or
disappointment resulting from and coverage of health care services.
Most countries in Africa are gaining reputation of poor service delivery, ineffectiveness, and
incompetence and high levels of corruption, although numerous initiatives have been put in place
in order to enhance service delivery, challenges relating to service delivery still abound,
nonetheless poor interdepartmental cooperation and lack of horizontal integration has hampered
effective local development planning and thereby contributed to crippling service deliveries
(Manyaka & Nkuna, 2014).
Service delivery in Africa faces difficult challenges such as shortage of health workers, increased
caseloads for health workers due to migration of skilled health personnel and the double burden
of disease and the HIV/AIDS scourge that affect both the general population and health
personnel, shortage/low motivation of health workers. Moreover, Inappropriate quality of service
delivery results in loss of customer lives, revenue, material resources, time, morale, staff,

3
recognition, trust and respect and individual and communities' apathy towards health services, all
of which contribute to lowered effectiveness and efficiency of service provider (Mohapatra et al.,
2010).
According to WHO (2013) any country that has unhealthy population bounds to suffer in the
implementation of development program to improve the quality life of its citizens. Each country
needs to offer quality health services and it is important to recognize that a healthy population is
better disposed to achieving the productivity that is needed so as to increase and sustain
continued growth of the country’s economy (Andaleeb, 2015).
Service delivery needs responsiveness by service providers, managers, and policy makers to be
answerable, to provide enforcement, and to make relevant organizational changes in order to
make services “people-centred” (Gonzalez Asis & Woolcock, 2015) . Mcloughlin and Batley
(2012) propose viewing service provision as a two-way process “in which services are formed
by, and formative of, state-society relations and processes of state building,” and placing service
provision in a broad question of control “that is, how and by whom is control exercised over
which services are delivered to whom.”. Improving the level of basic service delivery is partly a
question of resources but it is also a question of governance and allocation.
When an organization tries to offer service to customers, it is time for management to exercise
leadership. Leaders should become the role models for the rest of the staff and manifest behavior
that demonstrate what is expected from employees in relation to the service delivery. In addition,
during a time of service delivery, management needs to send positive messages about the service
itself (Auerbach & Silverstein, 2003). Some sort of reinforcement is necessary to produce
service delivery; Management should be very active in instituting reinforcement tactics even

4
those that are costless such as verbal reinforcement or altering its structure and policy by simply
writing new rules and procedures.
The Kenyan health service delivery system is organized into 6 levels of care that fits into four
tiers. Each level has specified scope health services that it should provide to its populace. Tier 1
community units, Tier 2 dispensaries and health Centres, Tier 3 County health facilities (Sub
County and County referral hospital) and Tier 4 national referrals (Njuguna, 2015).
Health services are provided through a network of over 4,700 health facilities countrywide, with
the public sector system accounting for about 51 percent of these facilities while 49 percent is
accounted for by the private sector. The public health sector consists of the national referral
hospitals, county referral hospitals, Sub-county hospitals, health centres, and dispensaries. Health
services are integrated as one goes down the hierarchy of health structure from the national level
to the county levels (Chodzaza & Gombachika, 2013).
Since the government cannot fully meet the health needs of its citizens, its effort to offer health
service is supplemented by privately owned and operated hospitals and clinics and faith-based
organizations’ hospitals and clinics, which together provide between 30 and 40 percent of the
hospital beds in Kenya. Depending on their comparative advantage, Non- Governmental
Organizations, Faith Based Organizations and community-based organizations (CBOs)
undertake specific health services.
In most developing countries in Africa, in Kenya, premature deaths and preventable diseases still
inflict a high toll in communities and its people because there inadequacy in access to basic
health services is affecting distinct regions, areas, communities, and social groups in these
countries (Ajayi & Tokon, 2009). Most public hospitals in the recent past have witnessed
employee dissatisfaction presented in terms of refusal to offer services due to failure of payment

5
of dues, poor working environment, inadequate infrastructure and lack of commitment by the
management to engage with employees. This gap in service delivery in public hospitals has led
to unwarranted suffering by the patients who lay their hopes on the services offered by these
hospitals.
Meru County is one of the Forty Seven (47) counties of Kenya strategically located east of Mt.
Kenya, whose peak cuts through the outskirt of its southern boundary. The county has a total
area of 6,936.2Km2 out of which 972.3Km2 is gazetted forest. The county borders five counties;
to the North it borders Isiolo County, to the East Tharaka/Nithi County, to the South West Nyeri
County and to the West Laikipia County. The County’s population growth rate is estimated at
2.1 per cent per annum. The projected population of the county in 2018 is 1,635,264, consisting
of 808,596 males and 826,668 females (Kenya National Bureau of Statistics [KNBS], 2009).
Health Services provision at the County Level is centred around the tenets described by both the
Kenya Essential Package of Health Services (KEPH) and Schedule IV of the Kenya Constitution
2010. These two key documents define mandates/roles/responsibilities for interventions and
service delivery of the health system. The county has twenty three sub-county hospitals and one
referral hospital (Meru County Data, 2017)

6
1.2 Statement of the Problem
Health is anchored in Vision 2030 under social pillar in which the country’s aim is to provide an
efficient integrated and high quality affordable health care for all citizens with a priority being
given to preventive care at the community and household levels using a decentralized national
health care system strategy (Government of Kenya [GOK], 2007). The health policy 2014-2030
spells out the organization of health services delivery system and what should be provided at the
specific hospitals, geared towards strengthening the referral mechanism in place (Njuguna,
2015).
The Sub- County Health Facilities (Levels 4) managed by the county is mandated to; offer
comprehensive patient diagnostic, medical, surgical and rehabilitative care, including
reproductive health services; specialized outpatient services; and Facilitate, and manage referrals
from lower levels, and other referral(Ministry of Health , 2014). Despite this, patients still
prefer accessing services from the county referral hospital (level 5) due to several challenges at
the sub county hospitals.
A study done by (Makheti, 2017) reveals that Sub County Hospitals in Meru lack of
equipment and drugs forcing health workers to rely on conventional diagnosis further putting
patients in danger of misdiagnosis. Another report by the ministry of Health done in 2013
on service availability and readiness assessment mapping, showed that the County
Hospitals offered a higher percentage of services delivery e.g. pharmaceuticals ,clinical
laboratory, maternity which accounted for 70%, 85% and 74% respectively (GoK, 2013). This
has caused an increased and continued congestion and strain on the County Referral Hospital
thus hampering quality of care Despite the tremendous efforts by the government to improve
the referral system in Kenya in order to improve efficiency in the health system and health
outcomes, service delivery remain a

7
big challenges impeding access to equitable, quality and responsive health services by the
populace equity quality services. Should the problem of underutilization health services in the
Sub -County Hospitals continue, the County and the country at large might not be able to achieve
its health goal of attaining the highest standards of health by the year 2030 (Njuguna, 2015).
A need therefore arises to investigate as to whether the Sub County Hospitals in Meru County
are delivering services commensurate to the concerted effort by the county government to
provide cost-effective priority healthcare interventions and services to ensure affordable,
equitable, accessible and acceptable health services. Therefore, this study sought to assess the
factors influencing service delivery at the Sub County Hospitals in Meru County.
1.3 Purpose of the Study
The purpose of the study was to assess the factors influencing service delivery at Sub-County
Hospitals in Meru County, Kenya.
1.4 Specific Objectives
i. To determine the influence of staff on service delivery in sub-county hospitals in
Meru County.
ii. To assess the influence of facilities on service delivery in sub-county hospitals in
Meru County.
iii. To establish the influence of management practices on service delivery in sub-county
hospitals in Meru County.
iv. To evaluate the influence of Drugs procurement process on service delivery in sub-
county hospitals in Meru County.

8
1.5 Research Questions
i. What is the influence of staff on service delivery in sub-county hospitals in Meru
County?
ii. How do facilities influence service delivery in sub-county hospitals in Meru County?
iii. What is the influence of management practices on service delivery in sub-county
hospitals in Meru County?
iv. How does Drugs procurement process influence service delivery in sub-county hospitals
in Meru County?
1.6 Justification of the Study
The National and County Government since devolution have put efforts in trying to provide
equitable health services to its population in every corner of this country. This has not been
achieved because of several factors affecting the health sector which touches on all pillars of
health. Meru County is not an exception to this challenge with the fact that the County is still
experiencing mortalities and morbidity from communicable and non-communicable diseases.
Service delivery is a key pillar in ensuring access to safe and quality health services at all levels
of care.
Despite the challenges experienced by the County there is no evidence of studies investigating
the factors in influencing service delivery in Meru County especially at the Sub county
Hospitals. Identifying and addressing the barriers to utilization of services at the level 4
Hospitals is key to increasing access and utilization of services thereby strengthening the referral
system.
Various studies that have been carried out mainly focused on general public health issues, for
instance a study by (Njuguna, 2015) looked at utilization of maternal health services.
Many

9
other studies investigated aspects of Health information system, Human resources for Health
among others but none has been done on service delivery at the Sub County Hospitals. It is in
this regard that the researcher intended to carry out this study to determine factors influencing
service delivery at the Sub County Hospitals in Meru County.
1.7 Limitations of the Study
During data collection the researcher experienced challenges of accessing the sub-county
hospitals due to their remote location, this caused a delay in collecting data. However, to
overcome this challenge, the researcher prior planned before data collection to ensure easy and
timely access to the hospital this made data collection possible and easy.
Additionally, the researcher experienced a challenge of uncooperative respondents due to their
tight schedules at work and fear of feeling like the hospital is under investigation. The researcher
worked hard to avail more time and was patient in order to access the respondents during their
free time as well as surety of confidentiality and anonymity of the information shared.
1.8 Delimitations of the Study
The researcher experienced challenges of accessing the sub-county hospitals due to their remote
location; this caused a delay in collecting data. Nevertheless, to overcome this challenge, the
researcher prior planned before data collection to ensure easy and timely access to the hospital
this made data collection possible and easy.
Similarly, the researcher experienced a challenge of uncooperative respondents due to their tight
schedules at work and fear of feeling like the hospital is under investigation. The researcher
worked hard to avail more time and was patient in order to access the respondents during their
free time as well as surety of confidentiality and anonymity of the information shared.

10
1.9 Significance of the Study
The study was to determine which factors influence service delivery in Sub County Hospitals in
Meru County. The research findings were expected to provide current and adequate information
to the national, county government and other stakeholders on the status of service delivery in
public hospitals which would inform policy formulation thereby enabling design of evidence
based, cost effective interventions and strategies to ensure proper and safe services are delivered.
Moreover, the findings are beneficial to other researchers since is expected to provide a basis
upon which other related studies can be done.
1.10 Assumptions of the Study
The study assumes that the respondents were free, honest and gave the right information. It also
assumes that participants had a sincere interest in participating in the research and didn’t have
any other motive for participating in the study. The inclusion criterion of the sample is
appropriate and therefore, assures that the participants had all experienced the same or similar
phenomenon of the study.
1.11 Operational definition of terms.
Staffing factors: These are factors that entail training, experience and
compensation of health workers.
Healthcare facility factors: They include attributes of health care facility such as
equipped laboratories, geographical access and functional
ambulances
Drug supply processes: This is the process used by hospitals in procuring drugs
that include procurement process, procurement policy and
procurement planning.

11
Management practices: They refer to the activities managers engage in to ensure
the organization runs on a daily basis, these activities
include planning, supervision and staff motivation.
Public Health Hospital: A hospital which is owned by a government and receives
government funding
Health workers: Health workers are people whose job is to protect and
improve the health of their communities.
Experience: Knowledge or skills in a particular activity which one has
gained through having done that activity for a specified
span of time

12
CHAPTER TWO
LITERATURE REVIEW
2.1 Introduction
This chapter entails the review empirical and theoretical literature. In addition, it also contains
the conceptual framework of this study.
2.2. Service Delivery
2.2.1. Quality service
Quality is one of the things that consumers look for in an offer, which service happens to be one.
Quality can also be defined as the totality of features and characteristics of a product or services
that bear on its ability to satisfy stated or implied needs (Kotler et al., 2019). It is evident that
quality is also related to the value of an offer, which could evoke satisfaction or dissatisfaction
on the part of the user. Service quality in the management and marketing literature is the extent
to which customers' perceptions of service meet and/or exceed their expectations. Thus service
quality can intend to be the way in which customers are served in an organization which could be
good or poor.
Service quality is a multidimensional concept. There are differences between objective quality
and perceived quality. The service quality is derived from customers’ cognitive evaluations of a
service and viewed as a transaction-specific level or a global level (Boonlertvanich,
2019). The service quality is also the result of comparison between the expected services and
perceived services. The service quality as a global judgment or attitude relates to the
superiority of a

13
service. Service quality and customers’ value have direct effect on customers’ loyalty (Lai et al.,
2009). Providing a high level of service quality is very important for service providers to
compete with other peers (Kemp & Rotmans, 2005).
In India a study was conducted to examine whether the service quality of Indian commercial
banks increases customers’ satisfaction that fosters customers’ loyalty (Lenka et al., 2009). The
unique integration of the resources and capabilities is the essence of overall service innovation
(Kowalkowski & Kindström, 2014). Service innovation can be equated with the creation
of new value propositions by means of developing existing or creating new practices and/or
resources (Skalen et al., 2015).
While studying the link of service quality, customers’ satisfaction and loyalty was investigated in
the context of six casinos in Macau to provide membership to customers. For instance, the chain
effect was investigated in a health setting, but conditional in the casino context (Shi et al., 2014).
In a relevant study in the post office context to investigate the relationship between the service
quality of postal services and customers’ loyalty with customers’ satisfaction as a mediating
variable. In other words, the research mentioned above highlights the existence of causal
relationships among service quality, satisfaction and loyalty (Moez & Gharbi, 2012).
An investigation into the link between service quality, value, satisfaction and behavioural
intentions in a public sector bank in India and one of their results states that “ Service quality was
found to significantly impact on customer satisfaction and value perceptions”.
The good quality of service will convincingly client to repeat the demand of service. It show
customer behavioural towards service provider. The quality of service that fulfils customer
expectation will gain the customer loyalty. This intention will make customers' favourable
inclination a service relative to other firms offering the same service (Kaura et al., 2015).

14
2.2.2. Accessible Service
As costs and demand for healthcare services rise, access to care is becoming more challenging
globally (Byrne & Callaghan, 2014). Many healthcare systems have also been reported to have
demand versus capacity issues that are extending wait times for care services, and in many cases
deny access. Despite the efforts to improve the systems, numerous healthcare systems around the
globe are faced with huge challenges in accommodating the high demand for healthcare services
as a result of acute workforce shortages, infrastructure limitation, patient locations and cost. In
its submission, proclaim that over one billion population globally lack access to healthcare
systems, from amenities to caregivers (Deloitte, 2014).
Globally, steps have been taken by some countries to address healthcare issues in order to
enhance patient access to care. From workforce shortage perspective, in the United States for
instance, employment in the healthcare sector has risen drastically, and it is expected to increase
to 11.9 percent in 2018. Australia on the other hand has launched a General Practice Training
program to increase the number of trainee general practitioners to 600 by 2014, while numerous
countries have identified the need to invest in healthcare infrastructure as a priority (Byrne &
Callaghan, 2014).
2.2.3. Affordable service
Poverty has been identified as being the greatest threat to health. The poor, who use public
facilities, have less access to healthcare than the more affluent, who are often covered by medical
aid insurance (Swinnerton, 2006). Health services should not only be accessible but should
include physical accessibility and affordable, as substantiated by the United Nations(Yamin et
al., 2003).

15
Statistical relationship between the health status of the poor and that of the wealthy was
established. It was identified that chronic diseases such as asthma, smoking and abuse of alcohol
were more prevalent amongst the poor than the rich; poorer areas are still plagued by a high
burden of disease (Bradshaw & Steyn, 2001). To further substantiate this finding, Stellenberg et
al. (2008) found a statistical relationship between the health status and the socioeconomic level
of the coloured people of the Western Cape. The use of health services may alter, depending on
where the individual lives. Patient factors may be more important than supply factors in
explaining the differential use of health services (Heyden et al., 2003).
2.3 Influence of Management Practices
2.3.1 Staff motivation
Health-care service managers need to have skills, knowledge and expertise required to fulfil day-
to-day responsibilities. Some of these skills and responsibilities include the requirement to
develop and maintain professional standards, procedures, and policies for various institutional
activities (Hamoud et al., 2016). They are also responsible for developing and expanding
programs for scientific research, preventive medicine, medical & vocational rehabilitation, and
community health welfare. Excellent, assertive communication skills, both verbal and written,
are paramount to a leader's ability to carry out an effective healthcare operation. Information
Communication Technology skills are also essential as healthcare machinery and information
systems continue to evolve (Harrison et al., 2010).
2.3.2 Planning
The motivating concept underlying employees’ incentives is to foster employees to put in more
effort to improve organisations performance, (Imberman, 2015). Motivation is one of the
factors influencing the work attitude of any establishment. To learn how to motivate employees

16
to execute assigned duties and responsibilities in the organisation is the objective of work
motivation. Motivation is a set of courses concerned with a kind of strength that boosts
performance and directs towards accomplishing some definite targets (Shoraj & Llaci, 2015).
These explanations show that to achieve positive goal, employees must be adequately active and
their objective clearly stated. Organisational growth, rest on identification factor analysis that
ascertains the success of the organization (Kennedy & Chew-Graham, 2014).
In a study to investigate managers’ perception of customer expectations in hotel industry in
Kenya. The results revealed that assurance, empathy and tangibles were regarded as the most
important factors affecting service quality (Kiange, 2011). Moreover, the findings established
that customers have the highest expectations on promptness of service, accuracy of transactions
and security issues. The researcher advised managers to prioritize on attention to details and
promptness in addressing customer complaints. The researcher noted that customers‟
expectations and perceptions are subjective and the findings can only be generalized to a pre-
defined market and economic scenarios (Rungtusanatham et al., 2010).
The study on motivational factors affecting professional conduct in the workplace, evinced that
poor professional conduct has been put forward as a precursor to low morale and is said to lead
to poor work performance. The low state of the spirits of a person or group as exhibited by
confidence, cheerfulness, discipline, and willingness to perform assigned tasks emanate from
lack of motivation and failure by Employers to address employee needs, drives and capabilities,
(Buhr et al., 2020). Financial incentives are preferred by the junior staff, because they perceived
non-financial incentives as not a motivational technique.
Although not denying the strength of financial incentives per se, their limited ability to resolve
complex problems in areas have seen support from complementary non-financial incentives

17
(Iyke et al., 2014). Consequently, they may not be effective if they are the only method used in
the public sector (Chaix et al., 2000).
It has been documented by many that the motivation approach has helped to improve efficiency
and employee motivation and their collective capabilities enhances employee performance
(Iqbal & Waseem, 2012). These lead to maximum productivity, but how best to get
employees committed to their work in accomplishing organisational goal has been the main
concern of managers (Iyoke et al., 2014). Intrinsic factors are considered to be those rewards (or
outcomes) that derive directly from or are inherently connected to the job/task, such as
recognition, degree of autonomy and responsibility, sense of accomplishment and growth,
demanding and challenging job. Consequently, the individual receives the intrinsic rewards by
the very act of performance (Tetteh, 2015).
Reward influences positively on employee performance (Hameed et al., 2014). The obligation to
assess the impact of compensation meant that attracting and motivating employees for effective
performance has been a challenged. Compensation attracts, retain and help increase employee’s
performance. In a research to determine the motivational factors affecting employee motivation
and their relationship with the resulted employee performance outcome in Pakistan, and
disclosed that access to quality experience, good environmental working condition, positive,
alignment of employee skills and job need as well as incentive packages have a notable influence
on job performance (Javed & Javed, 2014).

18
CHAPTER THREE
RESEARCH METHODOLOGY
3.1 Introduction
This chapter describes the study methodology and materials that were used. It explains the study
design, study population, sampling procedures and sample size determination, data collection,
data management and analysis, lastly describes the ethical considerations for the study.
3.2 Research Design
The researcher adopted a descriptive cross-sectional study design. In a cross sectional study the
researcher gathers data just once (Sekaran & Bougie, 2010). This design is appropriate
for this study because it provides quantitative and qualitative description of facts, attitudes, or
opinions of a population by studying a sample of that population. From sample results, the
researcher has generalized or drawed inferences to the population (Creswell, 2003).
3.3 Study Site
The Study was conducted in Sub-County Hospitals in Meru County. Meru County is one of the
Forty Seven (47) counties of Kenya strategically located east of Mt. Kenya. The county has a
total area of 6,936.2Km2. The county borders five counties; to the North it borders Isiolo
County, to the East Tharaka/Nithi County, to the South West Nyeri County and to the West
Laikipia County. It spans the equator lying 0 0 6’ North and 0 01’ South and between latitudes 370
West and 380 East (Meru County, 2018). According to the Kenya National Bureau of Statistics,
the population in the county is 1,365,301 people (male-670,656, females-685,645) (KNBS,
2015). The county’s’ administrative structure comprises of nine recognised (9) sub-counties. The
9 sub-counties include: Imenti South, Meru Central, Imenti North, Buuri, Tigania East, Tigania
West, Igembe Central, Igembe South and Igembe North. There are a total of 498 facilities

19
covering all levels of health and out of this number, Sub County hospitals are 23. The county
also has 1872 health care workers distributed evenly across the county (Meru County, 2018).
3.4 Target population
Target population refers to the entire group of individuals, elements or groups studied (Orodho,
2009). Meru County has a total of 23sub-county hospitals that were involved in this study.
In each sub-county hospital there are five officers in the management of the facility. These
officers include In-charge of the sub-county hospital, head of Pharmacy, head of Nursing, head
of laboratory and head of Clinical services. Therefore the total target population for this study
consisted of one hundred and fifteen staff in all the sub-county hospitals. These officers oversee
service delivery in these sub county hospitals.
3.5 Sample Size Determination and Sampling Procedure
3.5.1 Sample Size Determination
Meru County has a total of 23 sub-county hospitals that were involved in this study. Every sub-
county hospital has five officers who are at the helm of running and managing them. These
officers include the In-charge of the sub-county hospital, head of Pharmacy, head of Nursing,
head of laboratory and head of Clinical services. These officers oversee service delivery in all the
sub county hospitals and are well versed with knowledge about service delivery. Therefore the
sample size of this study was 115 employees of the 23 sub county hospitals.
3.5.2 Sampling Procedure
These officers were purposively selected to participate in the study due to their positions,
specialist knowledge, capacity and understanding of health matters and variables under this
study. Purposive sampling is a form of non-probability sampling in which decision concerning
the individuals to be included in the sample are taken by the researcher, based upon a variety of

20
criteria which may include specialist knowledge of the research issue, or capacity and
willingness to participate in the research (Oliver, 2006). The sample size of the study will consist
of all the one hundred and fifteen officers from the twenty three sub-county hospitals.
3.6 Instrumentation.
In this study, the researcher collected data using a self-administered structured questionnaire.
The questionnaire was made up of questions formulated using a 5 point likert scale (SA-
Strongly Agree; A-Agreed; U-Undecided; SD-Strongly Disagree; D-Disagreed) where the
respondent chose the answer that suited their response. The questionnaire consisted of sections
that measured staff, facilities, drug procurement; management practices factors that influence
service delivery in the facilities.
To ensure reliability and validity of the instrument, the researcher pre-tested the questionnaire to
ensure that it was measuring what it was supposed to measure and that the wording was clear for
the respondents. Pre-testing of the questionnaires was done in the neighbouring isiolo county and
involved 10% of the sample size which was 12 respondents from the sub county hospitals.
3.6.1 Validity
Validity is often defined as the extent to which an instrument measures what it asserts to measure
(Cooper, 2005). Validity of a research instrument assesses the extent to which the instrument
measures what it is designed to measure (Robson, 2011). It is the degree to which the
results are truthful. So that it requires research instrument (questionnaire) to correctly measure
the concepts under the study (Pallant, 2011). It encompasses the entire experimental concept,
and establishes whether the results obtained meet all of the requirements of the scientific
research method. Qualitative research is based on the fact that validity is a matter of
trustworthiness, utility, and dependability (Zohrabi, 2013).Validity of research is an extent
at which

21
requirements of scientific research method have been followed during the process of generating
research findings. It is a compulsory requirement for all types of studies (Oliver, 2010).
Validity determines whether the research truly measures that which it was intended to measure or
how truthful the research results are (Golafshani, 2003).
3.6.2 Reliability
Reliability refers to whether an assessment instrument gives the same results each time it is used
in the same setting with the same type of subjects (Sullivan, 2011). It refers to a measurement
that supplies consistent results with equal values (Cooper, 2005). It measures consistency,
precision, repeatability, and trustworthiness of a research (Chakrabartty, 2013). It indicates
the extent to which it is without bias (error free), and hence insures consistent measurement cross
time and across the various items in the instruments (the observed scores). Reliability is used to
evaluate the stability of measures administered at different times to the same individuals and the
equivalence of sets of items from the same test (Kimberlin & Winterstein, 2008). The
better the reliability is perform, the more accurate the results; which increases the chance of
making correct decision in research. Reliability is a necessary, but not a sufficient condition for
the validity of research. In this study, the researcher will use Cronbach’s alpha to test the
reliability of the instrument. Cronbach’s alpha measures how consistently participants respond to
one set of items. Cronbach’s alpha is thought of as a sort of average of the correlations between
items. Cronbach’s alpha ranges from 0.0 to 1.0 (a negative alpha means probably there is need to
reverse some items). Since the late 1960s, the minimally acceptable measure of reliability has
been 0.70; in practice, though, for high-stakes questionnaires, aim for greater than 0.90.
A questionnaire is reliable and valid, if both α and β are greater than 0.77. Once the pre- test
study has been done, necessary amendments will be made to the questionnaire. The researcher

22
did not use the pre-test sample in the actual study since the pre-test was carried out among
participants who did not form part of the main study.
3.7 Methods of Data Collection.
Data was collected by use of a questionnaire which was administered by the researcher on the
basis of drop and pick once the respondent has finished filling it. To be allowed for data
collection, the researcher applied for research permit from national commission for science
technology and innovation. Moreover, Heads of departments (In charge of the sub-county
hospital, head of Pharmacy, head of Nursing, head of laboratory and head of Clinical services) in
the sub-county Hospitals was approached and recruited into the study. The purpose of the
research and procedure will be explained to them and those who will consent to participate will
be interviewed by the researcher and the assistants. Confidentiality will be assured by ensuring
that the names of the respondent do not appear anywhere in the questionnaire. The researcher
will ensure that no respondent will be issued with a questionnaire more than once by asking if
they had previously been issued with one.
3.7.1 Ethical Considerations
The researcher obtained an introduction letter from Kenya Methodist University that was used to
apply for research permit from National commission for science technology and innovation. This
research permit enabled the researcher to collect data from the various respondents.
The researcher also obtained Ethical clearance from the Ethics and Research Committee of
Kenya Methodist University and permission sought from the respective hospital administrations
before the study was conducted. The researcher explained the purpose of the research and those
who volunteered were given the responses after informed consent and voluntary participation.
The names of the officers were not be recorded and the officers s’ identities were not included

23
anywhere in the data collection sheets to maintain confidentially. All data collected was
protected during the study. During the entire process of carrying out this research, all ethical
considerations were made to ensure high levels of confidentiality, anonymity, respect for other
people’s property and objects as well as convenience of the respondents.

24
3.8 Operational measure of Variables
Operationalization refers to the process of developing indicators or items for measuring
constructs (Bhattacherjee, 2012). Operationalization of variables is shown in Table 3.1.
Objective Type
Variables
of Indicator Measuring of
Indicators
Scale Type of Analysis
To determine the
influence of staff on
service delivery
Independent Staff Training
Experience
Compensation
Interval
ordinal
Descriptive
Pearson’s r
stats,
To assess the influence
of
facilities on service
delivery
Independent Facilities Wards
Ambulances
Geographical
access.
Interval Descriptive
Pearson’s r
stats,
To establish the
influence of
management practices
on service delivery
To evaluate the influence
of Drugs procurement
process on service
delivery
Independent
Independent
Dependent
Manage
ment
practices
Drugs
procure
ment
process
Service
Planning
Supervision
Staff motivation
Procurement
process.
Procurement
policy
Procurement
planning
Quality
interval
Interval
Nomin
Descriptive
Pearson’s r
Descriptive
Pearson’s r
Descriptive
stats,
stats,
stats,
Delivery Accountability
and efficiency
Accessibility
al Regression
analysis.
Table 3.1
Operational measure of variable
3.9 Methods of data analysis.
To ensure confidentiality and anonymity, the data collection tools will not bear a participant’s
name or ethnicity and will be identified by the study code numbers. Once the data has been
transferred from the instrument to the computers, the instrument will be kept safe in a secure

25
lockable cabinet for future reference. The completed instruments will not be destroyed or thrown
away for at least 3 years after the completion of the research. Access to data about individual
participants will be restricted to the researcher, supervisors and any research assistants on a need-
to-know basis.
The data will be checked for consistency, coded appropriately, and entered into SPSS software
package version 21 for analysis. Preliminary analyses will be conducted and any inconsistency in
the data will identified and corrected. The data will be explored and general features displayed to
identify problem areas before commencing data analyses. Descriptive and inferential statistical
tests will be used in the analysis. The output will be presented in tables and charts.

45
CHAPTER FOUR
RESULTS AND DISCUSSION
4.1 Introduction
This chapter presents study findings of the analysed data as per research variables. This research
study sought to determine factors influencing service delivery at Sub-County Hospitals in Meru
County, Kenya. Specific objectives included: i) to determine the influence of staff, ii) to assess
the influence of facilities, iii) to establish the influence of management practices, and iv) to
evaluate the influence of drugs procurement process on service delivery in Sub-county Hospitals
in Meru County
4.2 Response Rate
In this study, the number of questionnaires administered were 115 and 84 were successfully
completed and returned making the response rate of 73%. See Table 4.1. Response rate of 50% is
fit for analysis and publishing, 60% is good while 70% is very good (Babbie, 2014).
Table 4.1
Study Response Rate
Response Frequency Percentage %
Respondents 84 73
Non-respondents 31 27
Total 115 100
4.3 Reliability Test Results
The reliability of the instrument is the ability to give clear and stable measurement. In this study
research, the reliability was carried out using Cronbach’s coefficient test alpha. Coefficient alpha
is normally used during a scale development with items that have several items. A Cronbach’s α
≥ 0.7 implies that the tool delivers a moderately decent measurement tool and therefore is

46
consistent (Flick, 2015). The reliability results shown in Table 4.2 confirmed the reliability of
the instrument with a least Cronbach’s alpha of >0.704.
Table 4.2
Reliability Test Results
Scale Cronbach’s Alpha Number of items
Service delivery 0.736 9
Staff 0.704 9
Facilities 0.804 9
Management Practices 0.763 9
Drugs Procurement Process 0.765 9
4.4 Demographic Characteristics of the respondent
The demographic characteristics of the respondents were collected. It was necessary to
investigate the relevance of age, level of education, gender and years worked and their influence
service delivery in Sub-County hospitals in Meru County, Kenya.
4.4.1 Gender of the respondents
It was necessary to investigate the relevance of age and their influence service delivery in Sub-
County hospitals in Meru County, Kenya. There were 84 respondents who participated in the
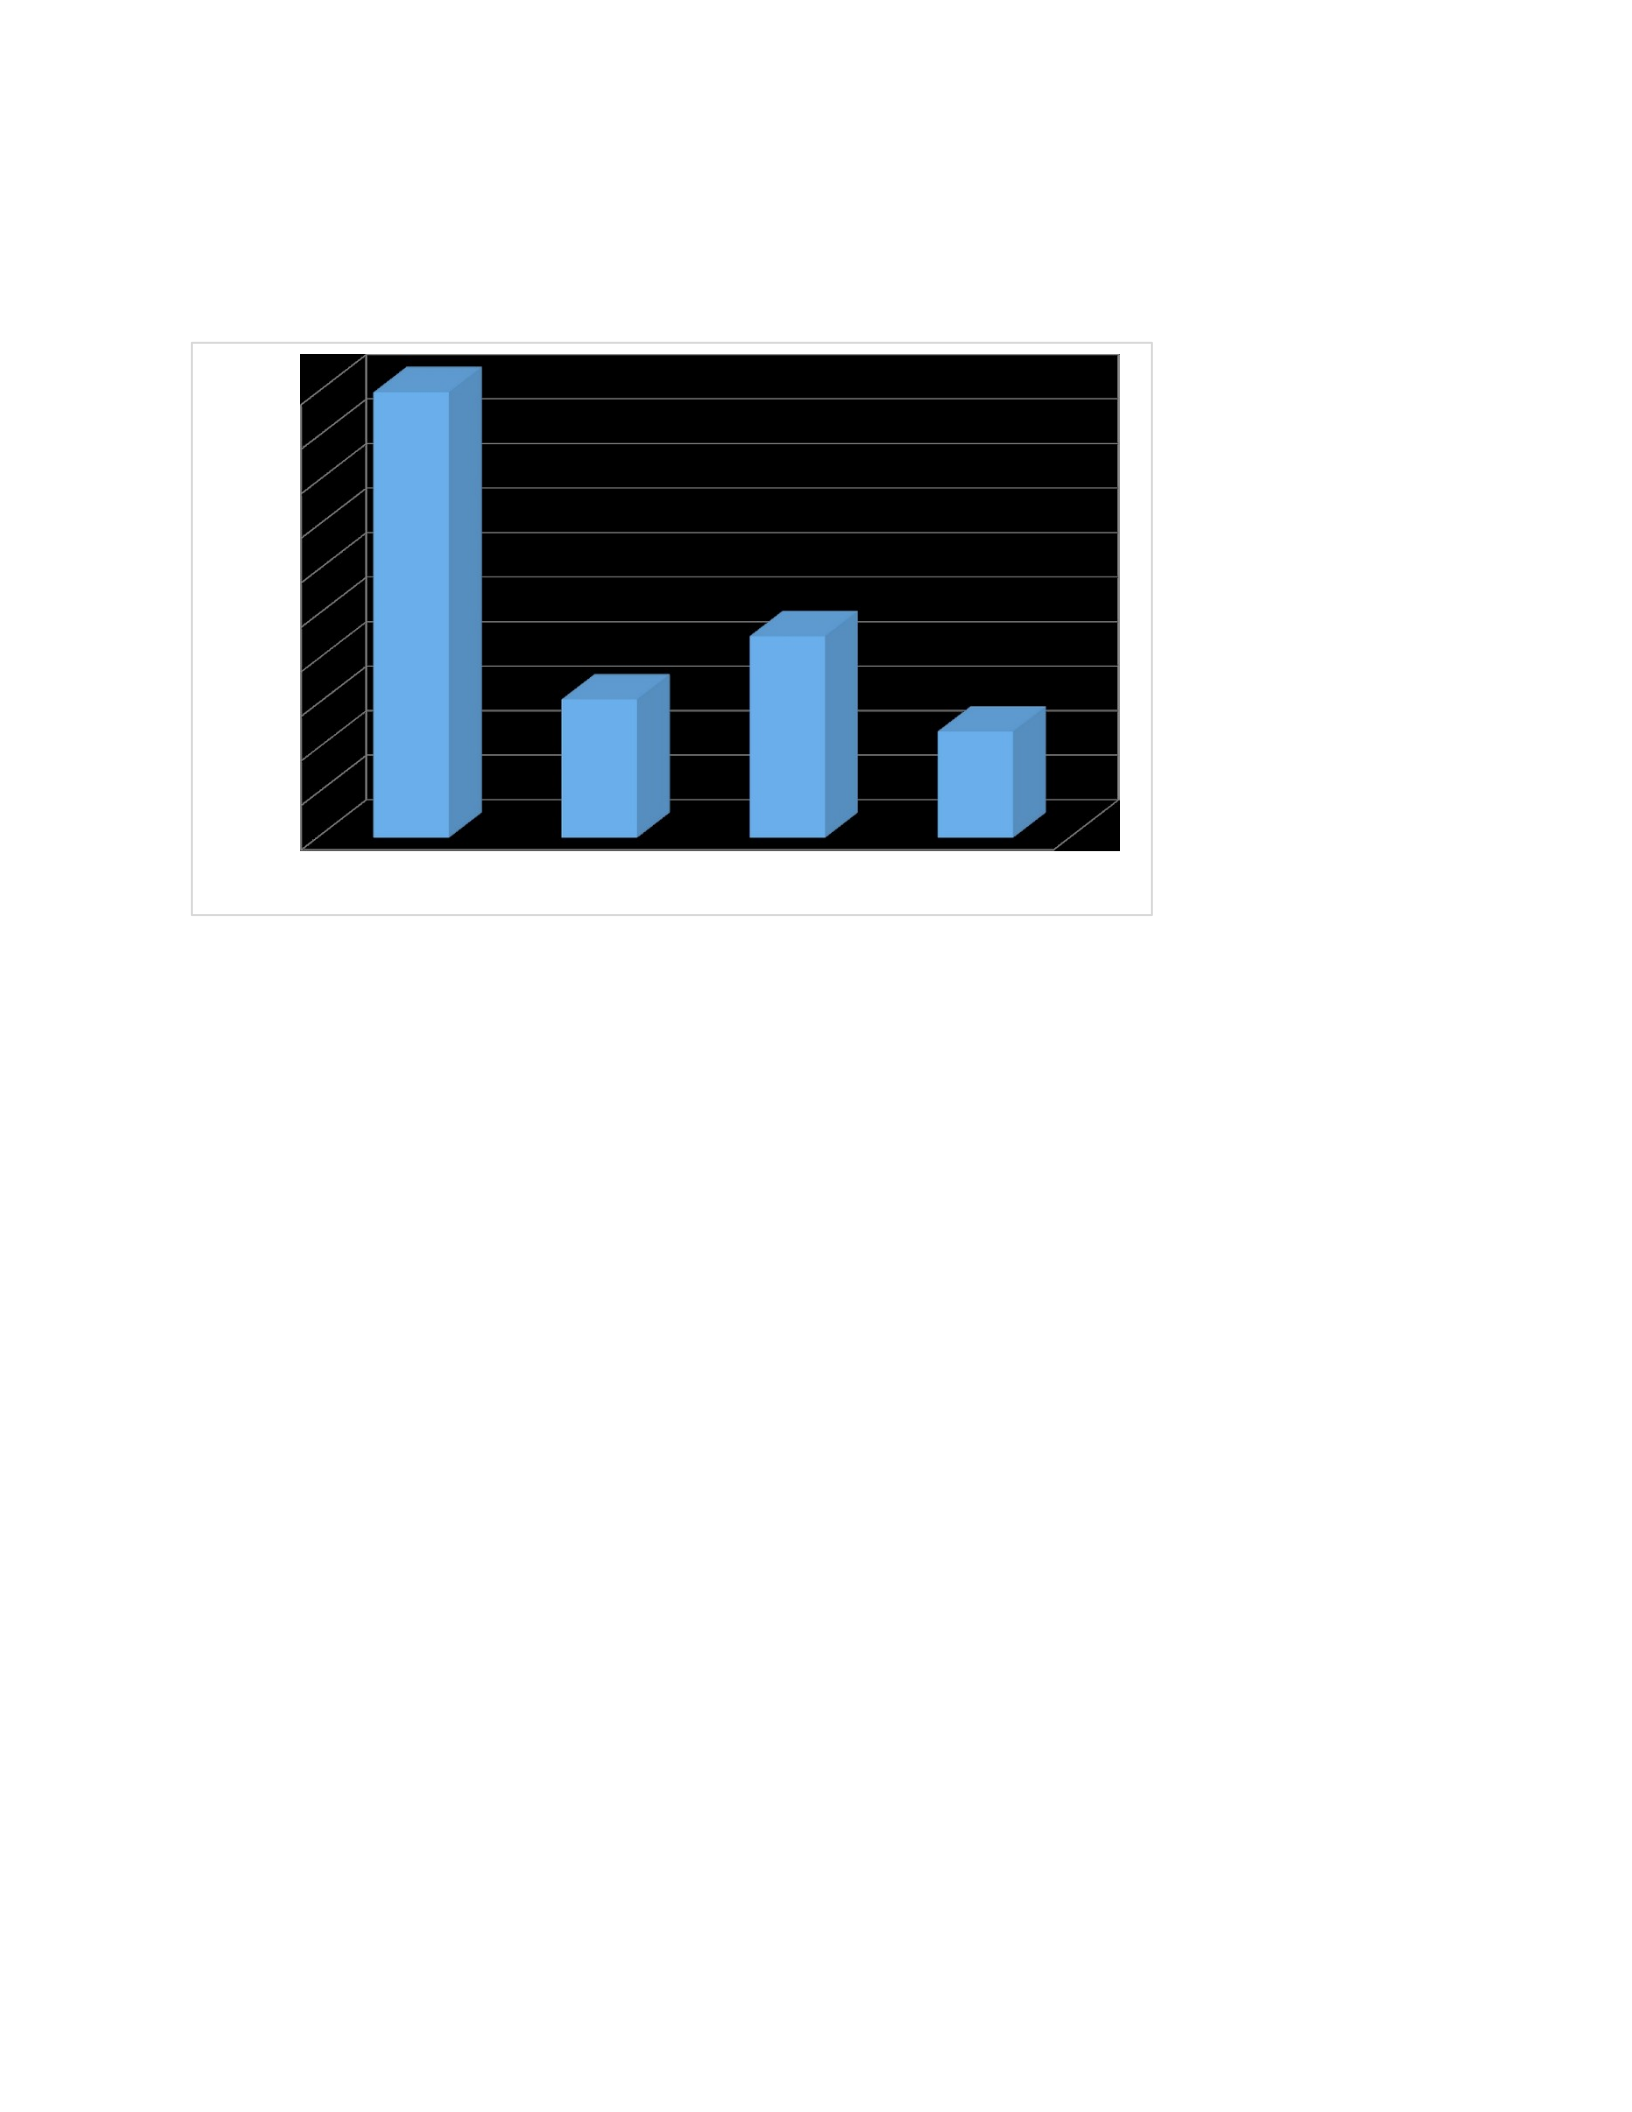
survey. All the respondents indicated their gender, most of the respondents (n=49, 58.3%) were
female while (n=35, 41.7%) were male as shown in figure 4.1

47
Figure 4.1
Gender of respondents
4.4.2 Age of the respondents
Similarly it was necessary to investigate the relevance of age and their influence service delivery
in Sub-County hospitals in Meru County, Kenya. Among the 84 respondents who participated in
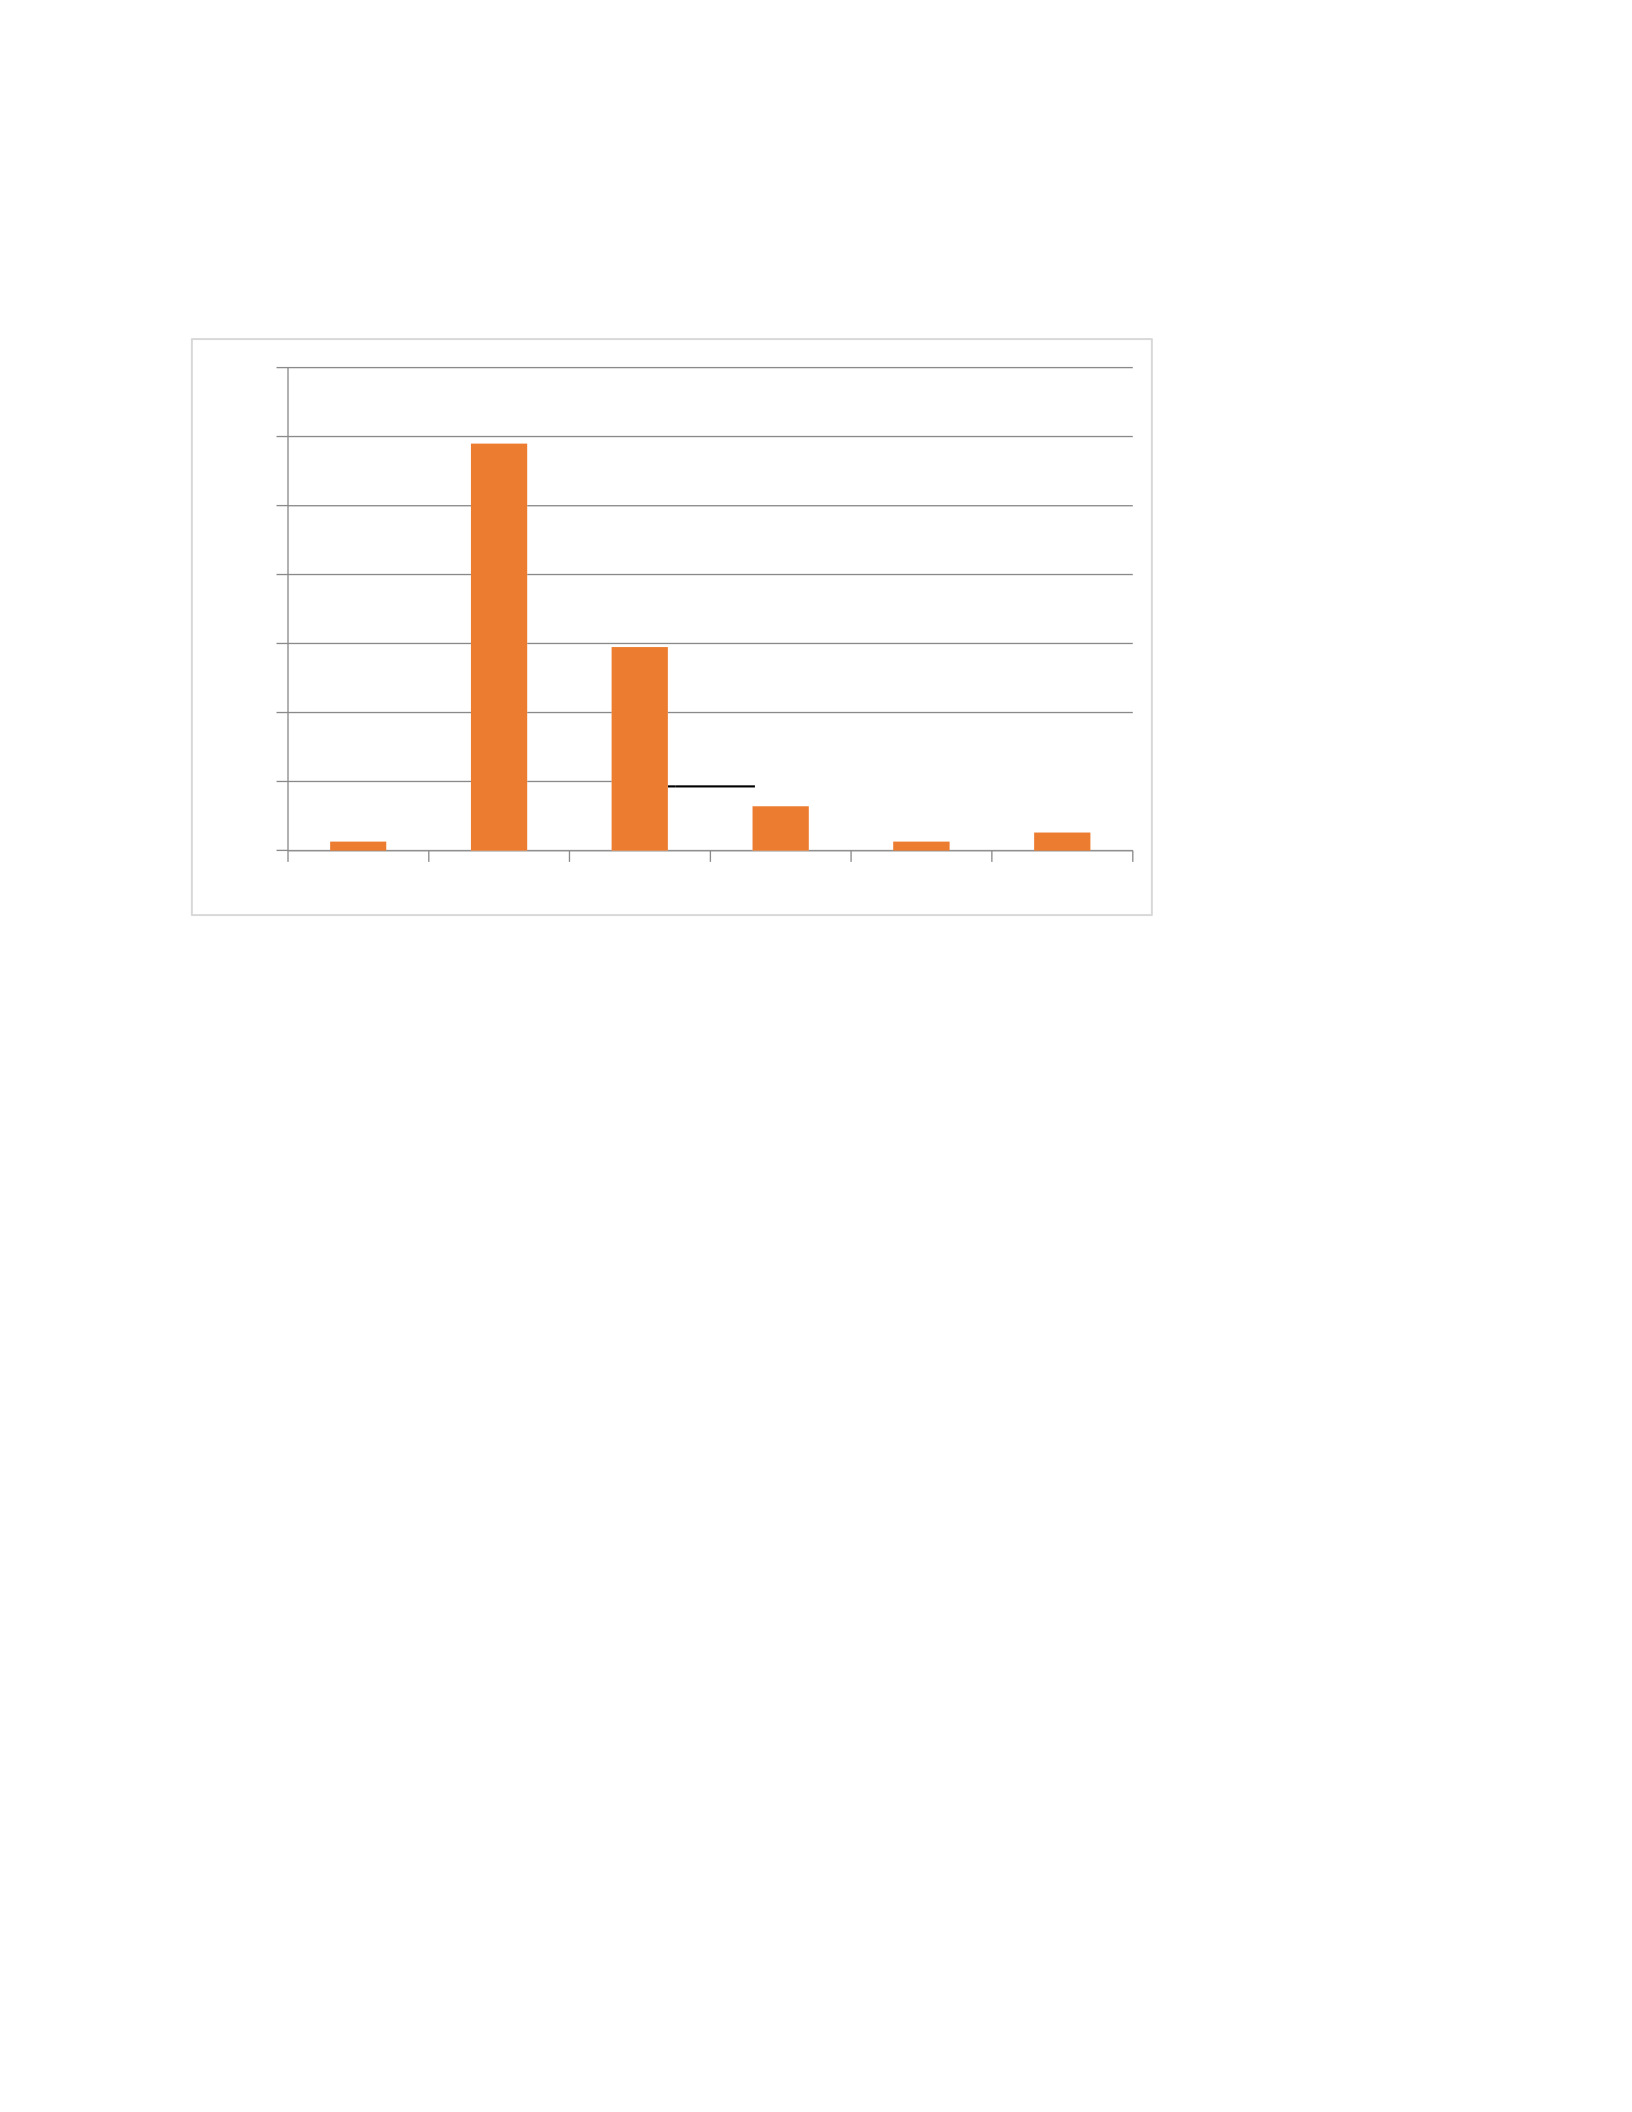
the survey, 77 of the respondents indicated their age-group. From figure 4.2 it is clear that most
of the respondents (n=35, 41.2%) were between age 31-40; (n=19, 22.4%) were between age 21-
30; (n=13, 15.4%) were between the age of 41-50; (n=10, 11.9%) were between age 51-60.
41.70%
58.30% Male
Female
48
Figure 4.2
Age of the respondents
4.4.3 Education level of the respondents
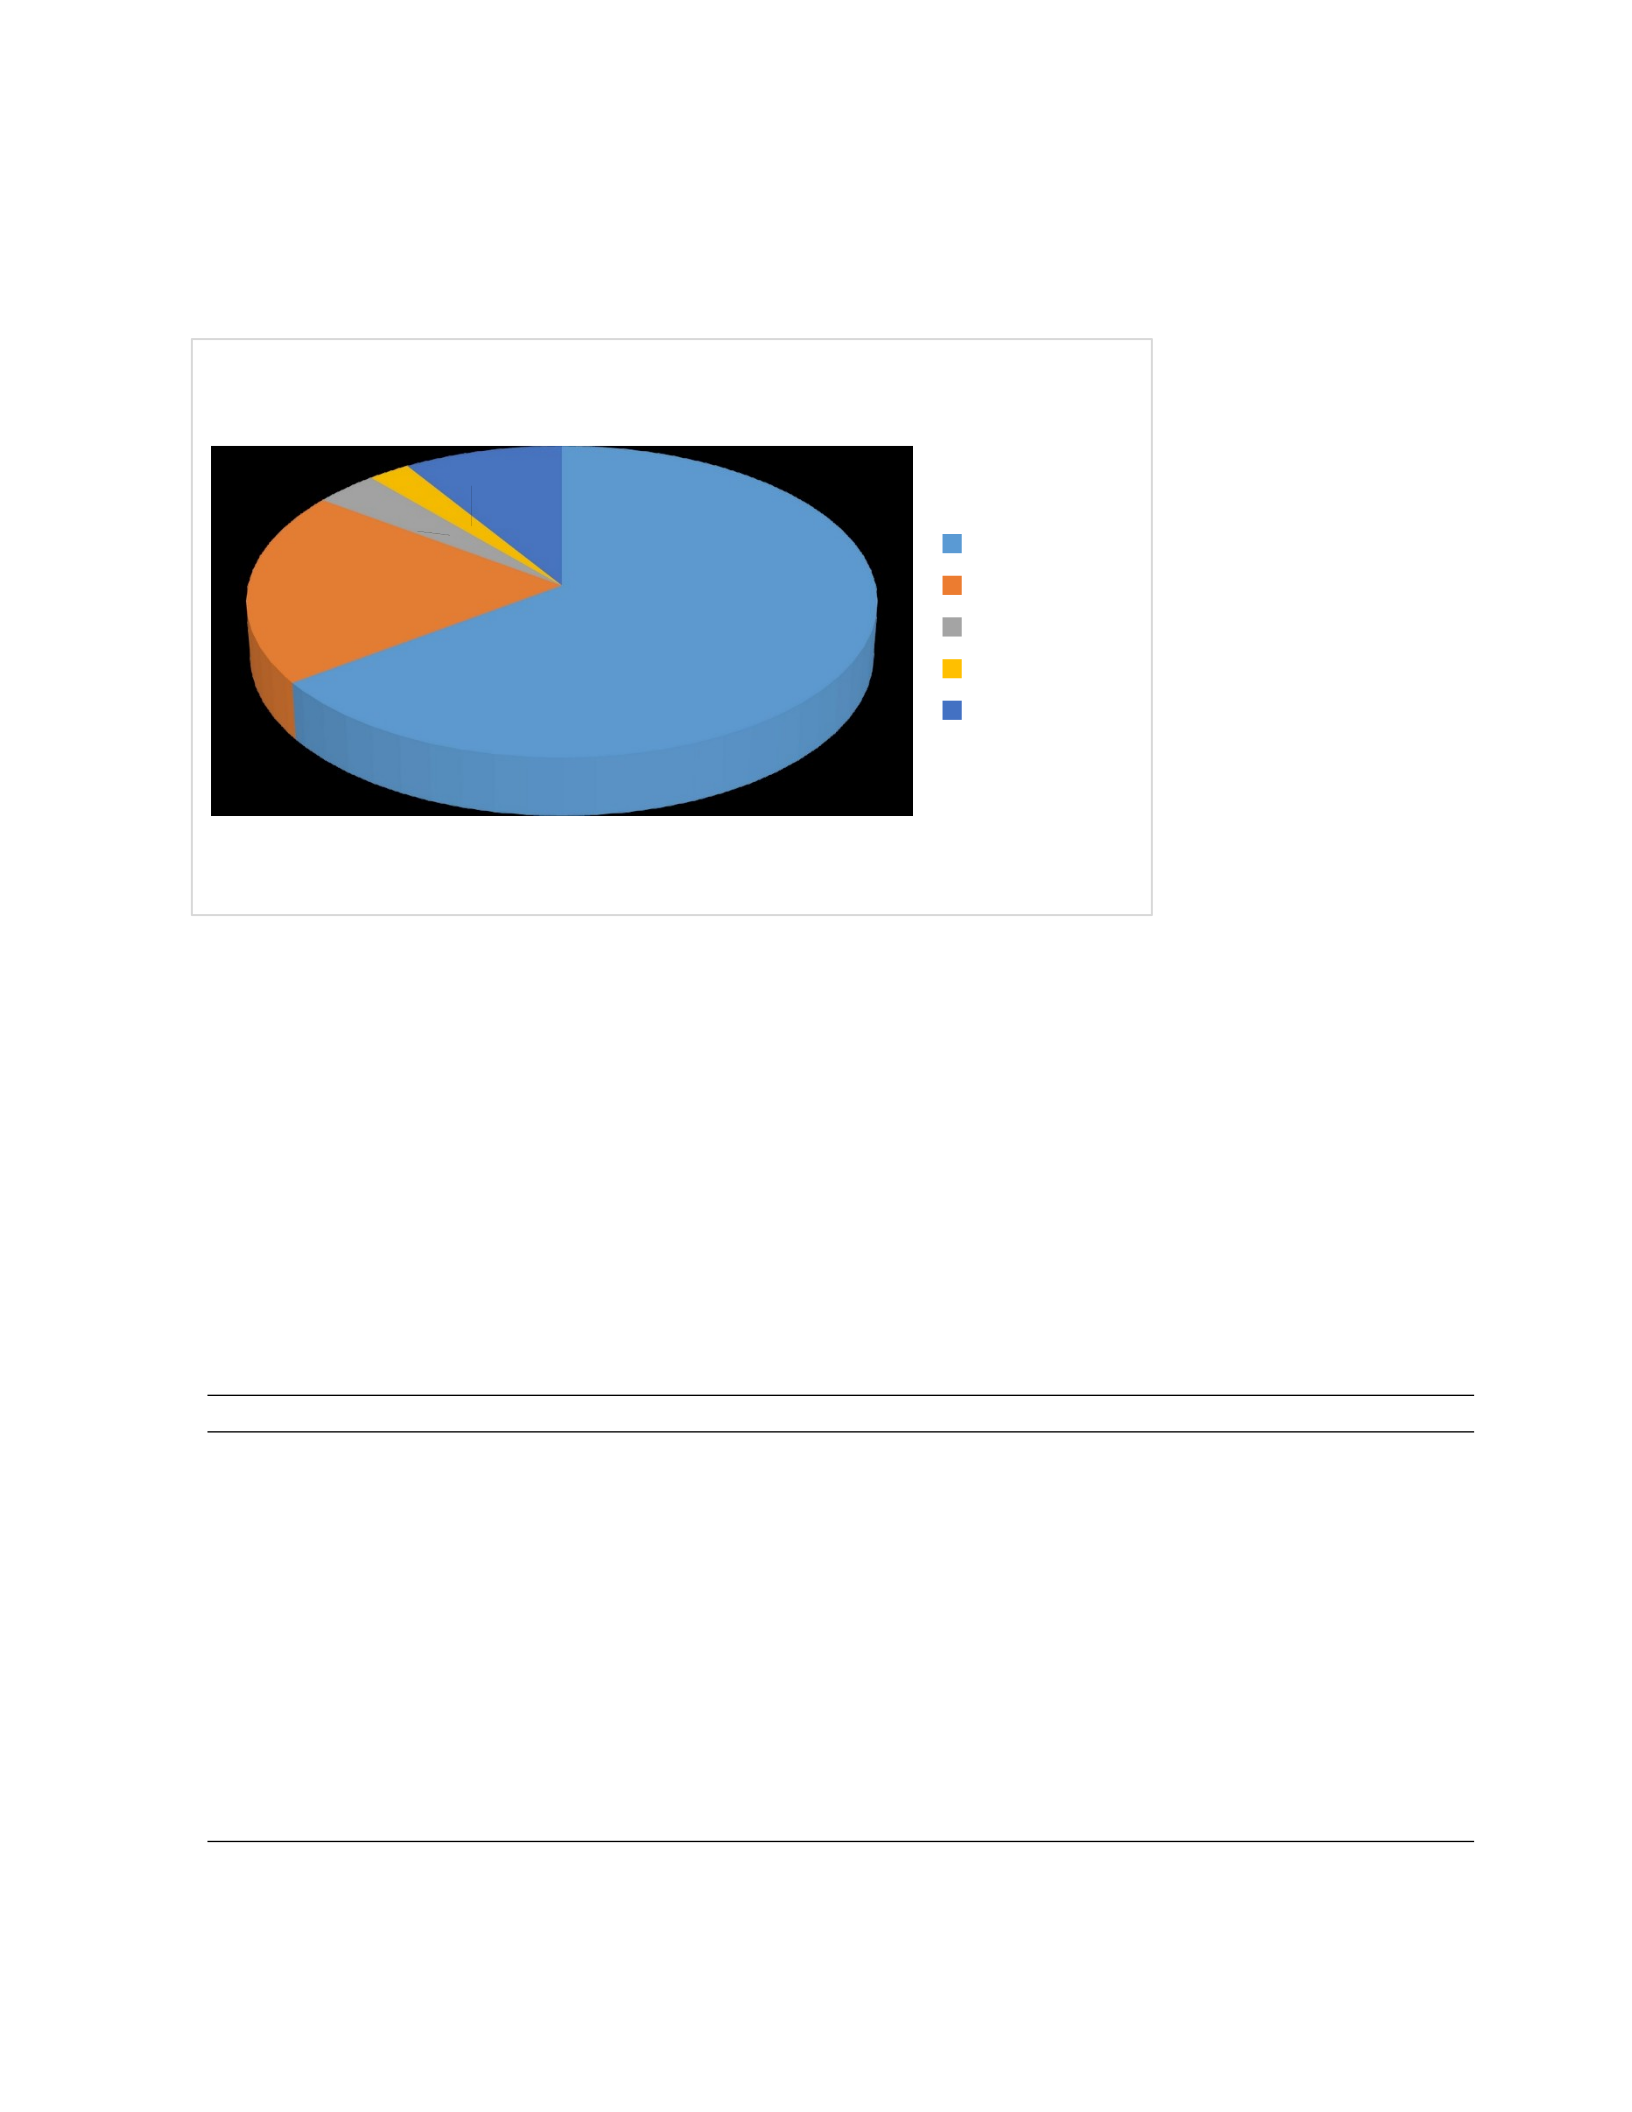
As shown in Figure 4.3 most of the respondents (n=46, 59.0%) indicated that they had gone up
to the Diploma level; (n=23, 29.5%) of the respondents had attained a Bachelor’s degree; (n=5,
6.4%) of the respondents had gone up to the certificate level ; (n=1, 1.3%) of the respondents had
attained a master degree and (n=1, 1.3%) of the respondents had gone to an extent of attaining a
PhD and (n=2, 2.6%) had other level of education, that is Hospitality Nutrition & Diatec.
50.00%
50%
45%
40%
35%
30%
25%
20%
15%
10%
5%
0%
22.60%
15.50%
11.90%
21-30 Years31-40 Years41-50 Years51-60 Years
49
Figure 4.3
Education level of the respondents
4.4.4 Years worked of the respondents
The number of respondents that participated in the survey was 84. Figure 4.4 indicate that most
of the respondents (n=55, 64.9%) indicated they had worked at the hospitals for 5 years and
below; (n=17, 20.1%) of the respondents indicated that they had worked at the hospitals for 6-11
years; three (3.6%) of the respondents indicated that for 11-20 years they had been working at
the hospital and (n=2, 2.4%) of the respondents had been at the hospital for 21 years and above.
70%
60%
59.00%
50%
40%
30%
29.50%
20%
10% 6.40%
1.30% 1.30% 2.60%
0%
Certificate DiplomaBachelorMasters PhD Other
s
50
Figure 4.4
Number of years worked by the respondents
4.5 Responses on Staff Issues in Sub-county Hospitals in Meru County
The first objective of the study was to determine the influence of staff on service delivery in sub-
county hospitals in Meru County. See results in Table 4.3.
Table 4.3
Responses on Staff Issues
Statements N Mean Std. Dev.
We always get an opportunity to advance our skills through 84 3.63 .875
CME/CPD
The hospital has a policy to support staff financially to 84 3.39 .761
further their education
The hospital always gives staff enough time for their training 84 3.55 .856
Most of the staff have many years of experience 84 2.71 .505
Staff are rotated in hospital sections to acquire experience 84 3.83 1.128
Staff are taken for benchmarking to build on their experience 84 3.98 .931
There is adequate compensation package for staff 84 2.74 .604
Compensation is always given in good time to staff 84 3.76 1.158
Compensation packages for all staff is competitive enough 84 3.90 1.001
2.40%9.00%
3.60%
20.10%
64.90%
0-5 Years
6-11 Years
11-15 Years
16-20 Years
21-30 Years

51
The respondents agreed that ccompensation package for all staff is competitive enough mean of
3.90, that they always get an opportunity to advance their skills through CME/CPD mean of
3.63, that staff are rotated in hospital sections to acquire experience mean of 3.83, and staff are
taken for benchmarking to build on their experience mean of 3.98. The respondents disagreed
that the hospital has a policy to support staff financially to further their education mean of 3.39,
most of the staff have many years of experience mean of 2.71, and that there is adequate
compensation package for staff 2.74.
This study found that there was great extent of agreements on staffing issues in all sub-county
hospitals in Meru County. Moreover, “Staff are taken for benchmarking to build on their
experience” is the attribute of staff that received the highest mean (M=3.98, SD= 0.931). This
means that management of these sub-county Hospitals was keen in taking their staff for
benchmarking since it was an important ingredient in service delivery compared to other
attributes such as “Most of the staff have many years of experience” which attained the lowest
mean (M=2.71, SD= 0.505) implying that many years of experience was not very key in service
delivery. This means that staffing issues like training and compensation package are critical in
delivery of healthcare services. These results are supported by the findings of a study conducted
by (Mwaniki & Dulo, 2008), in their study "Migration of Health Workers in Kenya: The
Impact on Health Service Delivery", training influences the capacity of health workers. High
quality and accessible health services cannot be delivered without sufficient numbers of well-
skilled, well distributed and well-managed health workers. In their study "Decentralizing
Kenya’s Health Management System: An Evaluation" observed that patient satisfaction is a
critical component in health care service delivery (Ndavi et al., 2009).

52
4.6 Responses on Hospital Facilities in Sub-county Hospitals in Meru County
The second objective of the study was to determine the influence of facilities on service delivery
in sub-county hospitals in Meru County. The results in Table 4.4 present the responses on state
of hospital facilities in sub-county hospitals in Meru County.
Table 4.4
State of Facilities in Sub-county Hospitals of Meru County
Statements N Mean Std. Dev.
The hospital has functional laboratories that serve patients 84 4.17 1.051
The hospital has state of the art laboratories 84 3.80 1.170
The hospital laboratories are always open to offer services 84 3.39 .761
The hospital is always accessible by road 84 3.58 .853
The proximity to the hospital is near to my home 84 2.75 .557
Hospitals are strategically located 84 3.85 1.135
Hospitals have functional ambulances 84 3.51 .898
Ambulances are well equipped 84 2.70 .555
Use of ambulances is affordable 84 3.79 1.162
The respondents agreed that the hospital has functional laboratories that serve patients scoring a
mean of 4.17, the hospital has state of the art laboratories scoring a mean of 3.80, hospitals are
strategically located 3.85, hospitals have functional ambulances 3.51, and the hospital is always
accessible by road 3.58. However the respondents disagreed that the hospital laboratories are
always open to offer services mean of 3.39, the proximity to the hospitals is near to their homes,
mean of 2.75, and that ambulances are well equipped mean of 2.70.
From the findings of this study, it was evident that the respondents agreed that the sub-county
hospitals had laboratory facilities. Aspects of facilities such as “the hospital has functional
laboratories that serve patients” had the highest mean (Mean=4.17; SD=1.051) implying that
functional laboratories were key in delivery services to patients. However, some aspects of
facilities such as “ambulances are well equipped” had the least mean (M=2.70; SD=0.557). This

53
meant that overall ambulances in sub-county hospitals were not well equipped which affects
service delivery. Overall, most respondents agreed that the hospital have laboratory facilities to
provide health services to all the patients. This implies that these laboratories in in usable state
and can meet the expectations of patients when they are receiving the services in the Hospital.
Results revealed that the hospitals are strategically located ad that hospitals are accessible by
road (Mean=3.85; SD=1.135 and Mean 3.58; SD=0.853) respectively. These results are
supported by Hall et al., (2006) who conducted a study in the Eastern Cape province of South
Africa with a view to understanding the impacts of transport to healthcare service delivery. Their
findings demonstrated not only the need for improved transport services in the delivery of health,
but also the importance of using the right type of vehicles. Their study also revealed that during
the rainy season, it was exceedingly difficult for delivery vehicles laden with drug supplies to
access health facilities largely because of poor road infrastructure running along hilly, often
broken and generally difficult terrain that characterize the province. In wet weather, these roads
become muddy and slippery. In fact, health transport problems are indeed most severe in the wet
season for most rural areas not only in South Africa but also in other developing countries (Gray
& Suleman, 1999). In a study done by Mobility and Health (2008) in Namibia, it was
demonstrated that transport for emergency cases comes at a higher cost for people living in rural
and largely marginalized areas. Very often, patients get too exhausted or die while waiting for
Ambulances, which take over three hours on average to report at the scene after a callout.
Lack of adequate and affordable transport services particularly in remote rural and marginalized
areas, under-girded by sound transportation infrastructure, are obstacles to achieving meaningful
service delivery. Clearly, without proper transport infrastructure and services, healthcare
facilities in these areas will remain under-serviced in terms of maintaining adequate levels of

54
medical supplies and retaining medical staff as well as eliciting confidence and therefore regular
utilization of the facilities by locals (Mashiri et al., 2016) .

55
CHAPTER FIVE
SUMMARY, CONCLUSION AND RECOMMENDATIONS
5.1 Introduction
This chapter presents the summary of the findings and it gives the conclusions and
recommendation of the study based on the objectives of the study. Specific objectives included
determining the influence of staff on service delivery in sub-county hospitals in Meru County,
assess the influence of facilities on service delivery in sub-county hospitals in Meru County,
establish the influence of management practices on service delivery in sub-county hospitals in
Meru County and evaluate the influence of Drugs procurement process on service delivery in
sub-county hospitals in Meru County.
5.2 Summary of the findings
This research study sought to determine factors influencing service delivery at Sub-County
Hospitals in Meru County, Kenya. In this study, the number of questionnaires administered
amounted to 115 out of which 84 were successfully completed and returned making the response
rate of 73%. To collect the data, the researcher used closed structured questionnaires that were
personally administered to all the sampled respondents. The target population for undertaking
this study included all Meru County 23 sub-county hospitals that were involved in this study. In
this study, data was analyzed using SPSS and findings were presented in the form of mean std
deviation, correlation and regression analysis. Findings revealed that majority of the respondents
were aged between 21-30 years and over. In addition this demographic result reveals that all of
the respondents have at least gone to school with over 50% having attained diploma.

56
5.2.1 Influence of staff on service delivery
The results confirmed that, on average the respondents agreed that staff have influence on
service delivery in sub-county hospitals in Meru County. Among the aspect agreed upon
included we always get an opportunity to advance our skills through CME/CPD, the hospital has
a policy to support staff financially to further their education, the hospital always gives staff
enough time for their training, most of the staff have many years of experience, staff are rotated
in hospital sections to acquire experience, staff are taken for benchmarking to build on their
experience, there is adequate compensation package for staff, Compensation is always given in
good time to staff and Compensation packages for all staff is competitive enough.
5.2.2 Influence of facilities on service delivery
The findings confirm that, on average the respondents agreed that facilities have influence on
service delivery in sub-county hospitals in Meru County. Among the aspect agreed upon
included hospital has functional laboratories that serve patients scoring, the hospital has state of
the art laboratories, the hospital laboratories are always open to offer service, the hospital is
always accessible by road, the proximity to the hospital is near to my home, Hospitals are
strategically locate, hospitals have functional ambulances, ambulances are well equipped while
use of ambulances is affordable.
5.2.3 Influence of management practices on service delivery
The study confirms that, on average the respondents agreed that the management practices have
influence on service delivery in sub-county hospitals in Meru County. Among the aspect agreed
upon included with the aspect of adequate resources are budgeted for implementing plans,
resources are availed for implementing plan, management follows and adhere to hospital,
management supervises staff adequately, there is sound relationship between staff and

57
supervisors, supervisors lead by examples to staff, hospital has a motivation policy for staff,
hospital management follows and adheres to motivation policy and management has various
reward systems for motivating employees.
5.2.4 Influence of drugs procurement process on service delivery
The results confirm that, on average the respondents agreed that the drugs have influence on
service delivery in sub-county hospitals in Meru County. Among the aspect agreed upon
included the aspect of drugs procurement process is flexible scoring, there is minimum lead time
during drugs procurement, there are adequate resources for drugs procurement, there is a hospital
policy for drugs procurement, procurement policies are adhered to during procurement, staff
understand and are familiar with procurement policy, hospital plans for procurement of drugs ,
hospitals adhere to procurement plans and procurement pans are flexible.
5.3 Conclusion
This study makes the following conclusion;
Staffs working in sub-county Hospitals in Meru County have an influence on service delivery in
these Hospitals and there was a strong and positive relationship between staff and service
delivery in sub-county Hospitals in Meru County. Moreover, Facilities in all sub-county
Hospitals in Meru County have an influence on service delivery. In addition, facilities have a
strong positive relationship with service delivery. Management practices influences service
delivery in all sub-county Hospitals in Meru County. Additionally, management practices were
found to have a strong and positive relationship with service delivery in all sub-county hospitals
in Meru County. Consequently, Drugs procurement process influences service delivery in all
sub-county Hospitals in Meru County. Moreover there was found a strong positive relationship

58
between drugs procurement process and service delivery in sub-county Hospitals in Meru
County.
5.4 Recommendations
This study recommends the following:
i. Management of Meru sub-county hospitals should provide adequate financial support
to their staff to enable them further their education in order to acquire more skills that
can empower them in delivering services to patients.
ii. Management of Meru sub-county hospitals should ensure that all sub-county hospitals
have adequate facilities that are in usable state to facilitate smooth service delivery to
all the patients.
iii. Management should follow and adhere to hospital plans, motivation policy and lead
by example to ensure smooth service delivery to the patients.
iv. Procurement department as well as Hospital administrator should always use and
adhere to drugs procurement plans to ensure there are drugs of right quality and
quantity in the Hospital at all given times to facilitate seamless service delivery.
5.5 Suggestions for further research
Carry out research study to widen the current knowledge on factors influencing service delivery
at Sub-County Hospitals in the neighbouring counties such as Tharaka Nithi so that the result is
obtained and used as a benchmark.

59
References
Ajayi, O. T. (2009). The advantage Project: Utilizing SMS to support evidence based medicine for
health practitioners in complex settings. John Hopkins University.
Ali, R. and Ahmed, M.S. (2009). The Impact of Reward & Recognition Programs on Employees
Motivation & satisfaction. An Empirical Study. International Review of Business Research
Papers, 5(4), 270-279. https://www.researchgate.net/publication/242422190
Auerbach, J. N. (2003). Police Accountability in Kenya; Seize the moment police as a service
Organization. African Human Rights Law Journal (AHRLJ), 3(2), 275-313.
https://www.ahrlj.up.ac.za/auerbach-j-n
Badaso, C. J. (2014). Challenges of Implementing Procurement Policy in States Corporations in Kenya.
European Journal of Business and Management,6(3), 56-61.
https://iiste.org/Journals/index.php/EJBM/article/view/10527
Basheka, B. (2004). Procurement planning and local governance in Uganda: A factor analysis approach.
Organisation. International Journal of Procurement Management,2(2), 191-209.
http://www.inderscience.com/link.php?id=23407
Bashuna, A. (2013). Factors affecting effective management of the procurement function at Nakuru
North Sub-County. World Academic Journal of Business & Applied Sciences (WAJBAS),1(7),
250-291. https://www.academia.edu/4683113/
Boonlertvanich, K. (2011). Effect of customer perceived value on satisfaction and customer loyalty in
bankingservice: The moderating effect of main bank status. International Journal of Business
Research, 11(6), 40-54. http://connection.ebscohost.com/c/articles/70065874/
Bradshaw, M., & Steyn, K. (2001). Poverty and chronic diseases in South Africa: Technical Report,
Cape Town and World Health Organization. Scandinavian Journal of Public Health, 37(2), 176–
186.https://doi.org/10.1177/1403494808100272Geneva: Medical Research Council.
Brown, C.A., Sohani, S.B., Khan, K. (2008). Antenatal care and perinatal outcomes in Kwale district,
Kenya. BioMed Central (BMC) Pregnancy Childbirth Journal, 8(2), 1-11.
https://doi.org/10.1186/1471-2393-8-2
Byrne, D., & Callaghan, G. (2014). Complexity theory and the social sciences. Routledge.
https://doi.org/10.4324/9780203519585
Chaix-Couturier, C., Durand-Zaleski, I., Jolly, D., & Durieux, P. (2000). Effects of financial incentives
on medical practice: results from a systematic review of the literature and methodological
issues. International journal for quality in health care : Journal of the International Society for
Quality in Health Care, 12(2), 133–142. https://doi.org/10.1093/intqhc/12.2.133
Chebat, J-C., & Kollias, P. (2000). The Impact of Empowerment on Customer Contact Employees’
Roles in Service Organizations. Journal of Service Research,3(1), 66-81.
https://doi.org/10.1177/109467050031005

60
Chodzaza, G. E. & Gombachika, H. S. H. (2013). Service quality, customer satisfaction and loyalty
among industrial customers of a public electricity utility in Malawi. International Journal of
Energy Sector Management, 7(2), 269-282. https://doi.org/10.1108/IJESM-02-2013-0003
Cromley, R. G., & Cromley, E. K. (2009). Choropleth map legend design for visualizing community
health disparities. International journal of health geographics, 8(52), 1-11.
https://doi.org/10.1186/1476-072X-8-52
Dacha, V. W., & Juma, D. (2018). Effect of stakeholder participation on the efficiency of the
procurement process in the public sector: a case of Jomo Kenyatta University of Agriculture And
Technology.strategic journal of business and change management,5(2), 1206-1230.
http://www.strategicjournals.com/index.php/journal/article/view/718/733
Delamater, P. L. (2013). Spatial accessibility in suboptimally configured health care systems: a modified
two-step floating catchment area (M2SFCA) metric. Health & place, 24(2013), 30–43.
https://doi.org/10.1016/j.healthplace.2013.07.012
Deloitte. (2014). 2014 Global health care outlook: shared challenges, shared opportunities.
https://www2.deloitte.com/content/dam/Deloitte/global/Documents/Life-Sciences-Health-Care/
dttl-lshc-2014-global-health-care-sector-report.pdf
Demirbag, Sahadev, & Akgul, K. (2012). Modeling quality commitment in service organizations: an
empirical study. European Journal of Marketing, 46(6), 790-810.
https://www.emerald.com/insight/content/doi/10.1108/03090561211214609/full/html
Duberg, C., & Mollén, M. (2010). Reward systems within the health and geriatric care sector.
Medicine, 3(2), 1-59. https://gupea.ub.gu.se/bitstream/2077/21844/1/gupea_2077_21844_1.pdf
Ellinger, Ellinger, & Bachrach, W. (2011). Measurement of organizational investments in social capital:
The service employee perspective. Journal of Business Research ,64(6), 572-578.
https://doi.org/10.1016/j.jbusres.2010.06.008
Finkle, L. (2011, January 4). Motivating Employee Performance Through Year-End
Bonuses. http://ezinearticles.com/?Motivating-Employee-Performance-Through-Year-End--
Bonuses&id=5658825
Fiszbein, A. D. (2011). Making Services Work. Indicators, Assessments, and Benchmarking of the
Quality and Governance of Public Service Delivery in the Human Development Sector. Policy
Research Working Paper. World Bank. https://doi.org/10.1596/1813-9450-5690
Furuta, M., & Salway, S. (2006). Women's position within the household as a determinant of maternal
health care use in Nepal. International family planning perspectives, 32(1), 17–27.
https://doi.org/10.1363/3201706
Gatrell, A. C. (2005). Complexity theory and geographies of health: a critical assessment. Social science
& medicine, 60(12), 2661–2671. https://doi.org/10.1016/j.socscimed.2004.11.002
Gittel, & Weiss. (2004). Coordination Networks Within and Across Organizations: A Multi-level
Framework. Journal of Management Studies, 41(1), 127- 153. https://doi.org/10.1111/j.1467-
6486.2004.00424.x

61
Gonzalez Asis, M. & Woolock, M. (2015).Operationalizing the Science of Delivery Agenda to Enhance
Development Results. World Bank. https://openknowledge.worldbank.org/handle/10986/23226?
locale-attribute=fr
Grönroos, C. &. (2011). Service as business logic: implications for value creation and marketing.
Journal of Service Management, 22(1), 5-22. https://doi.org/10.1108/09564231111106893.
Harrison, Bosse, & Phillips. (2010). Managing for stakeholders, stakeholder utility functions, and
competitive advantage. Strategic Management Journal,31(1), 58-74.
https://ssrn.com/abstract=1501885
Hatch, N., & Dyer, J. (2004). Human capital and learning as a source of sustainable competitive
advantage. Strategic Management Journal, 25(12). 1155 - 1178. https://doi.org/10.1002/smj.421
Heider, F. (1958). The Psychology of Interpersonal Relations. Psychology Press,
https://doi.org/10.4324/9780203781159
Heyden, V. d., Tafforeau, & Oyen, V. (2003). Socio-economic differences in the utilisation of health
services in Belgium . Health Policy , 65(2), 153–165. https://doi.org/10.1016/s0168-
8510(02)00213-0
Holmes, W., & Kennedy, E. (2010). Reaching emergency obstetric care: Overcoming the ‘second delay.
The Women’s and Children’s Knowledge Hub. 1(1), 1-4.
https://www.burnet.edu.au/publications/3465_reaching_emergency_obstetric_care_overcoming_
the_second_delay
Imberman, S. (2015). How effective are financial incentives for teachers” Linking teacher pay to student
performance has become popular, but evidence on its effectiveness is mixed. IZA World of
Labor, 2015(158), 1-6. https://wol.iza.org/articles/how-effective-are-financial-incentives-for-
teachers/long
Iqbal, J., (2012). Employee motivation in modern organization. Journal of contemporary research in
business, 4(3), 7-14. http://strategicjournals.com/index.php/journal/article/view/426/0
James, U. (2004). Public Policy and the African Environment: An Examination of the Theory and
practice of the planning process of the continent. In K. Kalu, (Ed.). (2004). Agenda Setting and
Public Policy in Africa. Routledge, https://doi.org/10.4324/9781315263151.
Javed, L., & Javed, N. (2013). An Empirical Study on the Factors That Affect Employee Motivation and
Their Relationship with Job Performance. International Journal of Management Sciences, 1(4),
114-124. https://ideas.repec.org/a/rss/jnljms/v1i4p2.html
Kaura, V., Durga Prasad, C.S. & Sharma, S. (2015). Service quality, service convenience, price and
fairness, customer loyalty, and the mediating role of customer satisfaction. International Journal
of Bank Marketing, 33(4), 404-422. https://doi.org/10.1108/IJBM-04-2014-0048
Kemp R., Rotmans J. (2005) The Management of the Co-Evolution of Technical, Environmental and
Social Systems. In: M., Weber, J. Hemmelskamp (eds) (33-35) Towards Environmental
Innovation Systems. Springer. https://doi.org/10.1007/3-540-27298-4_3

62
Kennedy, A., Rogers, A., Chew-Graham, C., Blakeman, T., Bowen, R., Gardner, C., Lee, V., Morris, R.,
& Protheroe, J. (2014). Implementation of a self-management support approach (WISE) across a
health system: a process evaluation explaining what did and did not work for organisations,
clinicians and patients. Implementation science, 9(129), 1-16. https://doi.org/10.1186/s13012-
014-0129-5
Ministry of Health (2010). Health managemnet information sysstem, Report for the 1996-1999 period.
Republic of Kenya.
Kiange, M. (2011). The relationship between service quality and customer satisfaction in the
telecommunication industry: Evidence from Nigeria. Broad Research in Accounting,
Negotiation, and Distribution,1(1), 88-100.
http://www.edusoft.ro/brand/RePEc/bra/journl/brand_1_ojo.pdf
Kotler, P. (2008). Principle of Marketing, (3rd ed). Pretence Hall .
Kotler, P., Keller, K. L., Goodman,G.,Brady, M., & Hansen, T. (2019). Marketing Management.
Pearson Education Limited.
Ladhari, R., Ladhari, I., & Morales, M. (2011). Bank service quality: comparing Canadian and Tunisian
customer perceptions. International Journal of Bank Marketing,29(3), 224-246.
https://doi.org/10.1108/02652321111117502.
Lai, F., Griffin, M., & Babin, B. J. (2009). How quality, value, image, and satisfaction create loyalty at a
Chinese telecom. Journal of Business Research,62(10), 980-986.
https://doi.org/10.1016/j.jbusres.2008.10.015
Lenka, U. Suar, D. & Mohapatra, P. K. (2009). Service quality, customer satisfaction, and customer
loyalty in Indian commercial banks. Journal of Entrepreneurship,18(1), 47-64.
https://doi.org/10.1177/097135570801800103
Lockwood, H. & Smits, S. (2011). Supporting Rural Water Supply. Moving toward a Service Delivery
Approach. Practical Action Publishing. https://www.jstor.org/stable/j.ctt1hj597s
Mamiro, R. (2010). Value for Money, The Limping Pillar in Public Procurement. Tanzania Procurement
Journal, 1(1), 4 -5.
http://ippa.org/images/PROCEEDINGS/IPPC4/01ComparativeProcurement /Paper1-2.pdf
Maund, L. (2001). An Introduction to Human Resource Management Theory & Practice. Macmillan.
Mburu, P.N., Zyl, H.V., & Cullen, M. (2013). Determinants of Customer Satisfaction in the Kenyan
Banking Industry. European Journal of Business and Management, 5(2), 155-161.
https://www.iiste.org/Journals/index.php/EJBM/article/view/3938
Mcloughlin, C. & Batley, R. (2012). The Effects of Sector Characteristics on Accountability
Relationships in Service Delivery (Working Paper No. 350). Overseas Development Institute.
https://ssrn.com/abstract=2209074 or http://dx.doi.org/10.2139/ssrn.2209074
Morçöl, G. (2012). A complexity theory for public policy. Routledge.

63
Mukucha, P. (2013). The Mediation Effects of Perceived Service Quality in The Relationship between
Employee Satisfaction and Customer Satisfaction. Journal of Studies in Accounts and
Economics, 1(3), 9-16. http://ijecm.co.uk/wp-content/uploads/2019/03/7314.pdf
Nichols, P. (2002). Regulating transnational bribery in times of globalization and fragmentation. The
Yale Journal of Internal law,24(1), 257-304.
https://digitalcommons.law.yale.edu/yjil/vol24/iss1/6/
Nyaboke, J., Arasa, R.., & Ombui, K. (2013). Effects of public procurement policies on organizational
performance: A case of Water Services Regulatory Board. International Journal of Social
Sciences and Entrepreneurship,1(5), 89-103.
https://www.ijsse.org/articles/ijsse_v1_i5_89_103.pdf
Obiero. (2008). The challenges in the implementation of the 2005 procurement act on the Kenyan
Ministry of Higher Education, Science and Technology. [Master's thesis University of Nairobi]
http://erepository.uonbi.ac.ke/handle/11295/63996
Oduor, C. (2013). Integrity in the Public Health Sector Service Delivery in Busia County. Institute of
Economic Affairs. https://media.africaportal.org/documents/Busia-Final-1.pdf
Pathmanathan, I., Liljestrand, J., Martins, J. M., de Silva, A., Lissner,C., Selvaraju, S., & Singh, P.
(2003). Investing in maternal health: Learning from Malaysia and Sri Lanka. The world bank
group. https://openknowledge.worldbank.org/handle/10986/14754
Ployhart, R. E. & Moliterno,T. P. (2011). Emergence of the human capital resource: A multilevel model.
Academy of Management Review, 36(1),127–150. https://www.jstor.org/stable/29765018
Rungtusanatham, M., Filippini, R. B. & Anderson, J. C. (2010). A replication study of a theory of
quality management underlying the Deming management method: insights from an Italian
context. Journal of Operations Management, 17(1), 77-95. https://doi.org/10.1016/S0272-
6963(98)00032-1
Rosann, S., & Barton, W. (2014). Adaptive Selling: Conceptualization, Measurement and Nomological
Validity. Journal of Marketing Research, 27(1),61-69. https://www.jstor.org/stable/3172551
Sarvadi, P. (2010, October ). The Best Ways to Reward Employees. Entrepreneur Magazine.
https://www.entrepreneur.com/article/75340
Schooner, & Whiteman. (2000). Purchase Cards and Micro Purchases. Public Procurement Law Review,
9(4), 148-170. https://doi.org/10.1108/JOPP-08-03 2008-B003
Singh, J. (2000). Performance productivity and quality of frontline employees in service
organizations. Journal of Marketing, 64(2), 15–34. https://doi.org/10.1509/jmkg.64.2.15.17998
Skålén, P., Gummerus, J., von Koskull, C., & Magnusson, P. (2015). Exploring value propositions and
service innovation: a service-dominant logic study. Journal of the Academy of Marketing
Science, 43(2), 137-158. https://doi.org/10.1007/s11747-013-0365-2

64
Sony, M. & Mekoth, N. (2012). A typology for frontline employee adaptability to gain insights in
service customisation: a viewpoint. International Journal of Services and Operations
Management, 12(4), 490-508. https://doi.org/10.1504/IJSOM.2012.047955
Stellenberg, E. L., Welmann, E. B., & Groenewald, J. C. (2008). Investigation into the relationship
between the socio-economic and health status of the coloured people of the Western Cape in an
urban setting. Curationis, 31(2), 50–59. https://doi.org/10.4102/curationis.v31i2.981
Swinnerton S. (2006). Living in poverty and its effects on health. Contemporary nurse, 22(1), 75–80.
https://doi.org/10.5172/conu.2006.22.1.75
Tetteh, K. I. (2015). The relationship between employees’ incentives and performance at Ghana oil
company limited in the southern zone of Ghana. Advances in Social Sciences Research Journal,
2(2), 1-5. https://doi.org/10.14738/assrj.22.952
Thomas, A., Spencer, J., & Perin, J. (2005). The effect of geographical and spatial behaviour on
healthcare utilization among the residents of a rural region. Health Service Research, 40(1),135-
155. https://doi.org/10.1111/j.1475-6773.2005.00346.x
Thompson,C. & Rampton, L. (2003). Human Resource Management. NewYork: Melbourne Press.
Torrington, D. & Stephen, L.H. (2008). Human Resource Management (7th ed.). Pearson Education
Limited.
World Health Organisation. (2014). The health of the people: what works: the African Regional Health
Report.https://www.afro.who.int/publications/african-regional-health-report-2014-health-people-
what-works
Wimonphan, P., & Nuttawuth, M. (2012). Is There a Link? Employee Satisfaction and Service Quality.
World Journal of Management,4(1), 82-92.
https://www.cscjournals.org/manuscript/Journals/IJBRM/Volume6/Issue3/IJBRM-187.pdf
Yamin. (2003). Not just a tragedy: Access to medications as a right under international law. Boston
University International Law Journal ,21(2), 325–371.
https://pubmed.ncbi.nlm.nih.gov/16514750/

65
Appendices
Appendix i: Letter of Introduction
Kenya Methodist University
P. 0 Box 267- 60200
MERU, Kenya
SUBJECT: INFORMED CONSENT
Dear Respondent,
My names are Jason Maingi Anampiu, I am an MSc student from Kenya Methodist University.
I am conducting a study titled: Factors influencing efficiency of service delivery in public
hospitals in Kenya: a case study of Meru County. The findings will be utilized to strengthen the
health systems in Kenya and other Low-in- come countries in Africa. As a result, countries,
communities and individuals will benefit from improved quality of healthcare services. This
research thesis is critical to strengthening health systems as it will generate new knowledge in
this area that will inform decision makers to make decisions that are research based.
Procedure followed
Participation in this study will require that I ask you some questions and also access all the
hospital’s department to address the six pillars of the health system. I will record the information
from you in a questionnaire check list. You have the right to refuse participation in this study.
You will not be penalized nor victimized for not joining the study and your decision will not be
used against you nor affect you at your place of employment. Please remember that participation
in the study is voluntary. You may ask questions related to the study at any time. You may refuse

66
to respond to any questions and you may stop an interview at any time. You may also stop being
in the study at any time without any consequences to the services you are rendering.
Discomforts and risks
Some of the questions you will be asked are on intimate subject and may be embarrassing or
make you uncomfortable. If this happens; you may refuse to answer if you choose. You may also
stop the interview at any time. The interview may take about 40 minutes to complete.
Benefits
If you participate in this study you will help us to strengthen the health systems in Kenya and
other Low-in- come countries in Africa. As a result, countries, communities and individuals will
benefit from improved quality of healthcare services. This field attachment is critical to
strengthening the health systems as it will generate new knowledge in this area that will inform
decision makers to make decisions that are research based.
Rewards
There is no reward for anyone who chooses to participate in the study.
Confidentiality
The interviews will be conducted in a private setting within the hospital. Your name will not be
recorded on the questionnaire and the questionnaires will be kept in a safe place at the
University.
Contact Information
If you have any questions you may contact the following supervisors:
i. Ms. Roselyn Kinyamu, Department of Health Systems Management – Riara
University.

67
ii. Dr. Wanja,Mwaura Tenambergen Chair of Department of Health Systems
Management - Kenya Methodist University, Nairobi Campus.
Participant’s Statement
The above statement regarding my participation in the study is clear to me. I have been given a
chance to ask questions and my questions have been answered to my satisfaction. My
participation in this study is entirely voluntary. I understand that my records will be kept private
and that I can leave the study at any time. I understand that I will not be victimized at my place
of work whether I decide to leave the study or not and my decision will not affect the way I am
treated at my work place.
Name of Participant…………………………………. Date…………………………..
Signature……………………………………….
Investigator’s Statement
I, the undersigned, have explained to the volunteer in a language s/he understands the procedures
to be followed in the study and the risks and the benefits involved.
Name of Interviewer………………………………………………Date…………………….
Interviewer Signature…………………………………………

68
Appendix ii: Research Questionaire
Section A: General Information:
(Please tick in the box provided)
1. Gender: Male [ ] Female [ ]
2. What is your age? ……………………………………....
3. Name of the hospital (Optional) ……………………………………..
4. Level of education
Certificate [ ] Diploma [ ] Bachelors [ ]
Masters [ ] PhD [ ] others (specify)……………..
5. How many years have you worked in this hospital? ……………………………………………..
Section B. Staff
Rate the following statements on staffing issues and how they influence service delivery.
Statement SA A U SD D
Training
We always get an opportunity to advance our skills through
CME/CPD
The hospital has a policy to support staff financially to further their
education
The hospital always gives staff enough time for their training
Experience
Most of the staff have many years of experience
Staff are rotated in hospital sections to acquire experience
Staff are taken for benchmarking to build on their experience
Compensation
There is adequate compensation package for staff
Compensation is always given in good time to staff
Compensation packages for all staff is competitive enough
SA- Strongly Agree; A-Agreed; U-Undecided; SD-Strongly Disagree; D-Disagreed

69
Section C. Facilities
Rate the following statements on facilities issues and how they influence service delivery.
Statement SA A U SD D
Equipped laboratories
The hospital has functional laboratories that serve patients
The hospital has state of the art laboratories
The hospital laboratories are always open to offer services
Geographical access
The hospital is always accessible by road
The proximity to the hospital is near to my home
Hospitals are strategically located
Ambulances
Hospitals have functional ambulances
Ambulances are well equipped
Use of ambulances is affordable
SA- Strongly Agree; A-Agreed; U-Undecided; SD-Strongly Disagree; D-Disagreed
Section D. Management practices
Rate the following statements on management practices issues and how they influence service
delivery.
Statement SA A U SD D
planning
Adequate resources are budgeted for implementing plans
Resources are availed for implementing plans
Management follows and adhere to hospital plans
Supervision
Management supervises staff adequately
There is sound relationship between staff and supervisors
Supervisors lead by examples to staff
Staff motivation
Hospital has a motivation policy for staff
Hospital management follows and adheres to motivation policy
Management has various reward systems for motivating employees
SA- Strongly Agree; A-Agreed; U-Undecided; SD-Strongly Disagree; D-Disagreed

70
Section D. Drugs procurement process
Rate the following statements on drugs procurement process and how they influence service
delivery.
Statement SA A U SD D
Procurement process
Drugs procurement process is flexible
There is minimum lead time during drugs procurement
There are adequate resources for drugs procurement
Procurement policy
There is a hospital policy for drugs procurement
Procurement policies are adhered to during procurement
Staff understand and are familiar with procurement policy
Procurement planning
Hospital plans for procurement of drugs
Hospitals adhere to procurement plans
Procurement pans are flexible
SA- Strongly Agree; A-Agreed; U-Undecided; SD-Strongly Disagree; D-Disagreed
Section E. services delivery
Rate the following statements on service delivery as a result of staff, facilities, management
practices and drugs procurement process
Statement SA A U SD D
Quality
Hospital services are effective in serving patients’ needs
Services offered in this hospital are safe to the patients
Services offered here are centered on the patient’s needs
Accountability and efficiency
Health services are well managed so as to achieve the core
elements described above with a minimum wastage of resources
Managers are allocated the necessary authority to achieve
planned objectives and held accountable for overall performance
and results
Health services are delivered in a timely manner to the patients
Accessibility
Services are directly and permanently accessible with no undue
barriers of cost, language, culture, or geography
Health services are close to the people, with a routine point of
entry to the service network at primary care level
Services may be provided in the home, the community, the

71
workplace, or health facilities as appropriate
SA- Strongly Agree; A-Agreed; U-Undecided; SD-Strongly Disagree; D-Disagreed
Thank you for your time

72
Appendix iv. Ethical clearance

73

74
Appendix v. Introduction letter from the University

75
Appendix vi. Research Licence

76

77
Appendix vii. Approval to collect data in Meru County

