


Demographic characteristics of patients.
The sample size was a total of 102 patients i.e 51 cases and 51 controls. The male to female
ratio for both the cases and controls was 1:3.4 with 13 males (25.5%) and 38 females (74.5%)
included in the study.
The mean age for cases was 54.14 years with a standard deviation of 5.74 and 55.75 years for
the controls with a standard deviation of 6.12. The age ranged from 45 to 64 years for both
cases and controls.
Table: Gender distribution of patients
Arm
Case Control Total
N %
n
%
n
%
Gender Female 38 74.5 38 74.5 76 74.5
Male 13 25.5 13 25.5 26 25.5
Table: Age distribution of patients
Age Control Case Total
Mean 54.14 55.75 54.94
Median 54.00 57.00 55.00
Minimum 45.00 45.00 45.00
Maximum 64.00 64.00 64.00
Standard Deviation 5.74 6.12 5.96
p-value 0.174
Duration of treatment for hypertensive patients
The mean duration of treatment was 5.75 years with the shortest treatment time being 3
months and the longest duration 20 years with a standard deviation of 5.02. The median was 3
years. This did not apply for controls. Thirty one of the patients (60.8%) had been treated for
five years or less,14 patients for 6-10 years while 6 patients (11.8%) were on treatment for
more than ten years.

Table. Duration of treatment
Duration of treatment for
hypertension Case Control Total
Mean 5.75 . 5.75
Median 3.00 . 3.00
Minimum .25 . .25
Maximum 20.00 . 20.00
Standard Deviation 5.02 . 5.02
p-value
-
History of tinnitus
Twenty hypertensive patients (39.2%) had tinnitus with only two (3.9%) of the controls
having tinnitus (p-value <0.0001), this was statistically significant. In 15 patients tinnitus was
in both ears, right ear in one and left ear in four. Seventeen of the patients with tinnitus in the
cases were female while 3 were male. Five of the hypertensive patients with tinnitus had
normal Bp , nine had BP grade 1 while 6 had BP grade 2. Five of the 20 patients (25%) with
tinnitus also had hearing loss.
Table: History of tinnitus
Arm
Case Control Total
N
%
n
%
N
% p-value
Tinnitus No 31 60.8 49 96.1 80 78.4 <0.0001
Yes 20 39.2 2 3.9 22 21.6
Physical Examination: Blood pressure measurement.
The mean blood pressure was 146/85 mmHg for cases and 125/79 for the controls with a p-
value of <0.0001, it was statistically different.
Among the patients with hypertension 18 out of 51 (35.3%) had well controlled BP, 22
(43.1%) had grade 1 hypertension and the other 11(21.6%) had grade 2 hypertension with the
highest systolic reading at 178mmHg and diastolic reading at 104 mmHg.
Table: Blood pressure findings
Arm
Case Control Total
N % N % N %
p-value
BP grade
Normal 18 35.3 51 100.0 69 67.6
<0.0001
Grade 1 22 43.1 0 .0 22 21.6
Grade 2 11 21.6 0 .0 11 10.8
Grade 3 0 .0 0 .0 0 .0
Pure tone audiogram
Among the hypertensive patients, 13 out of 51 (25.5%) had hearing loss with 5 having
bilateral hearing loss and 8 unilateral hearing loss giving a total of 18 individual ears out of
102 (17.65%). Ten out of the 13 patients (76.9%) had mild hearing loss, 2 (15.4%) had
moderate hearing loss, with 1 having profound hearing loss. Seven (13.7%) of the controls
had hearing loss. Four had bilateral hearing loss, hence 11 individual ears (10.8%). Six of the
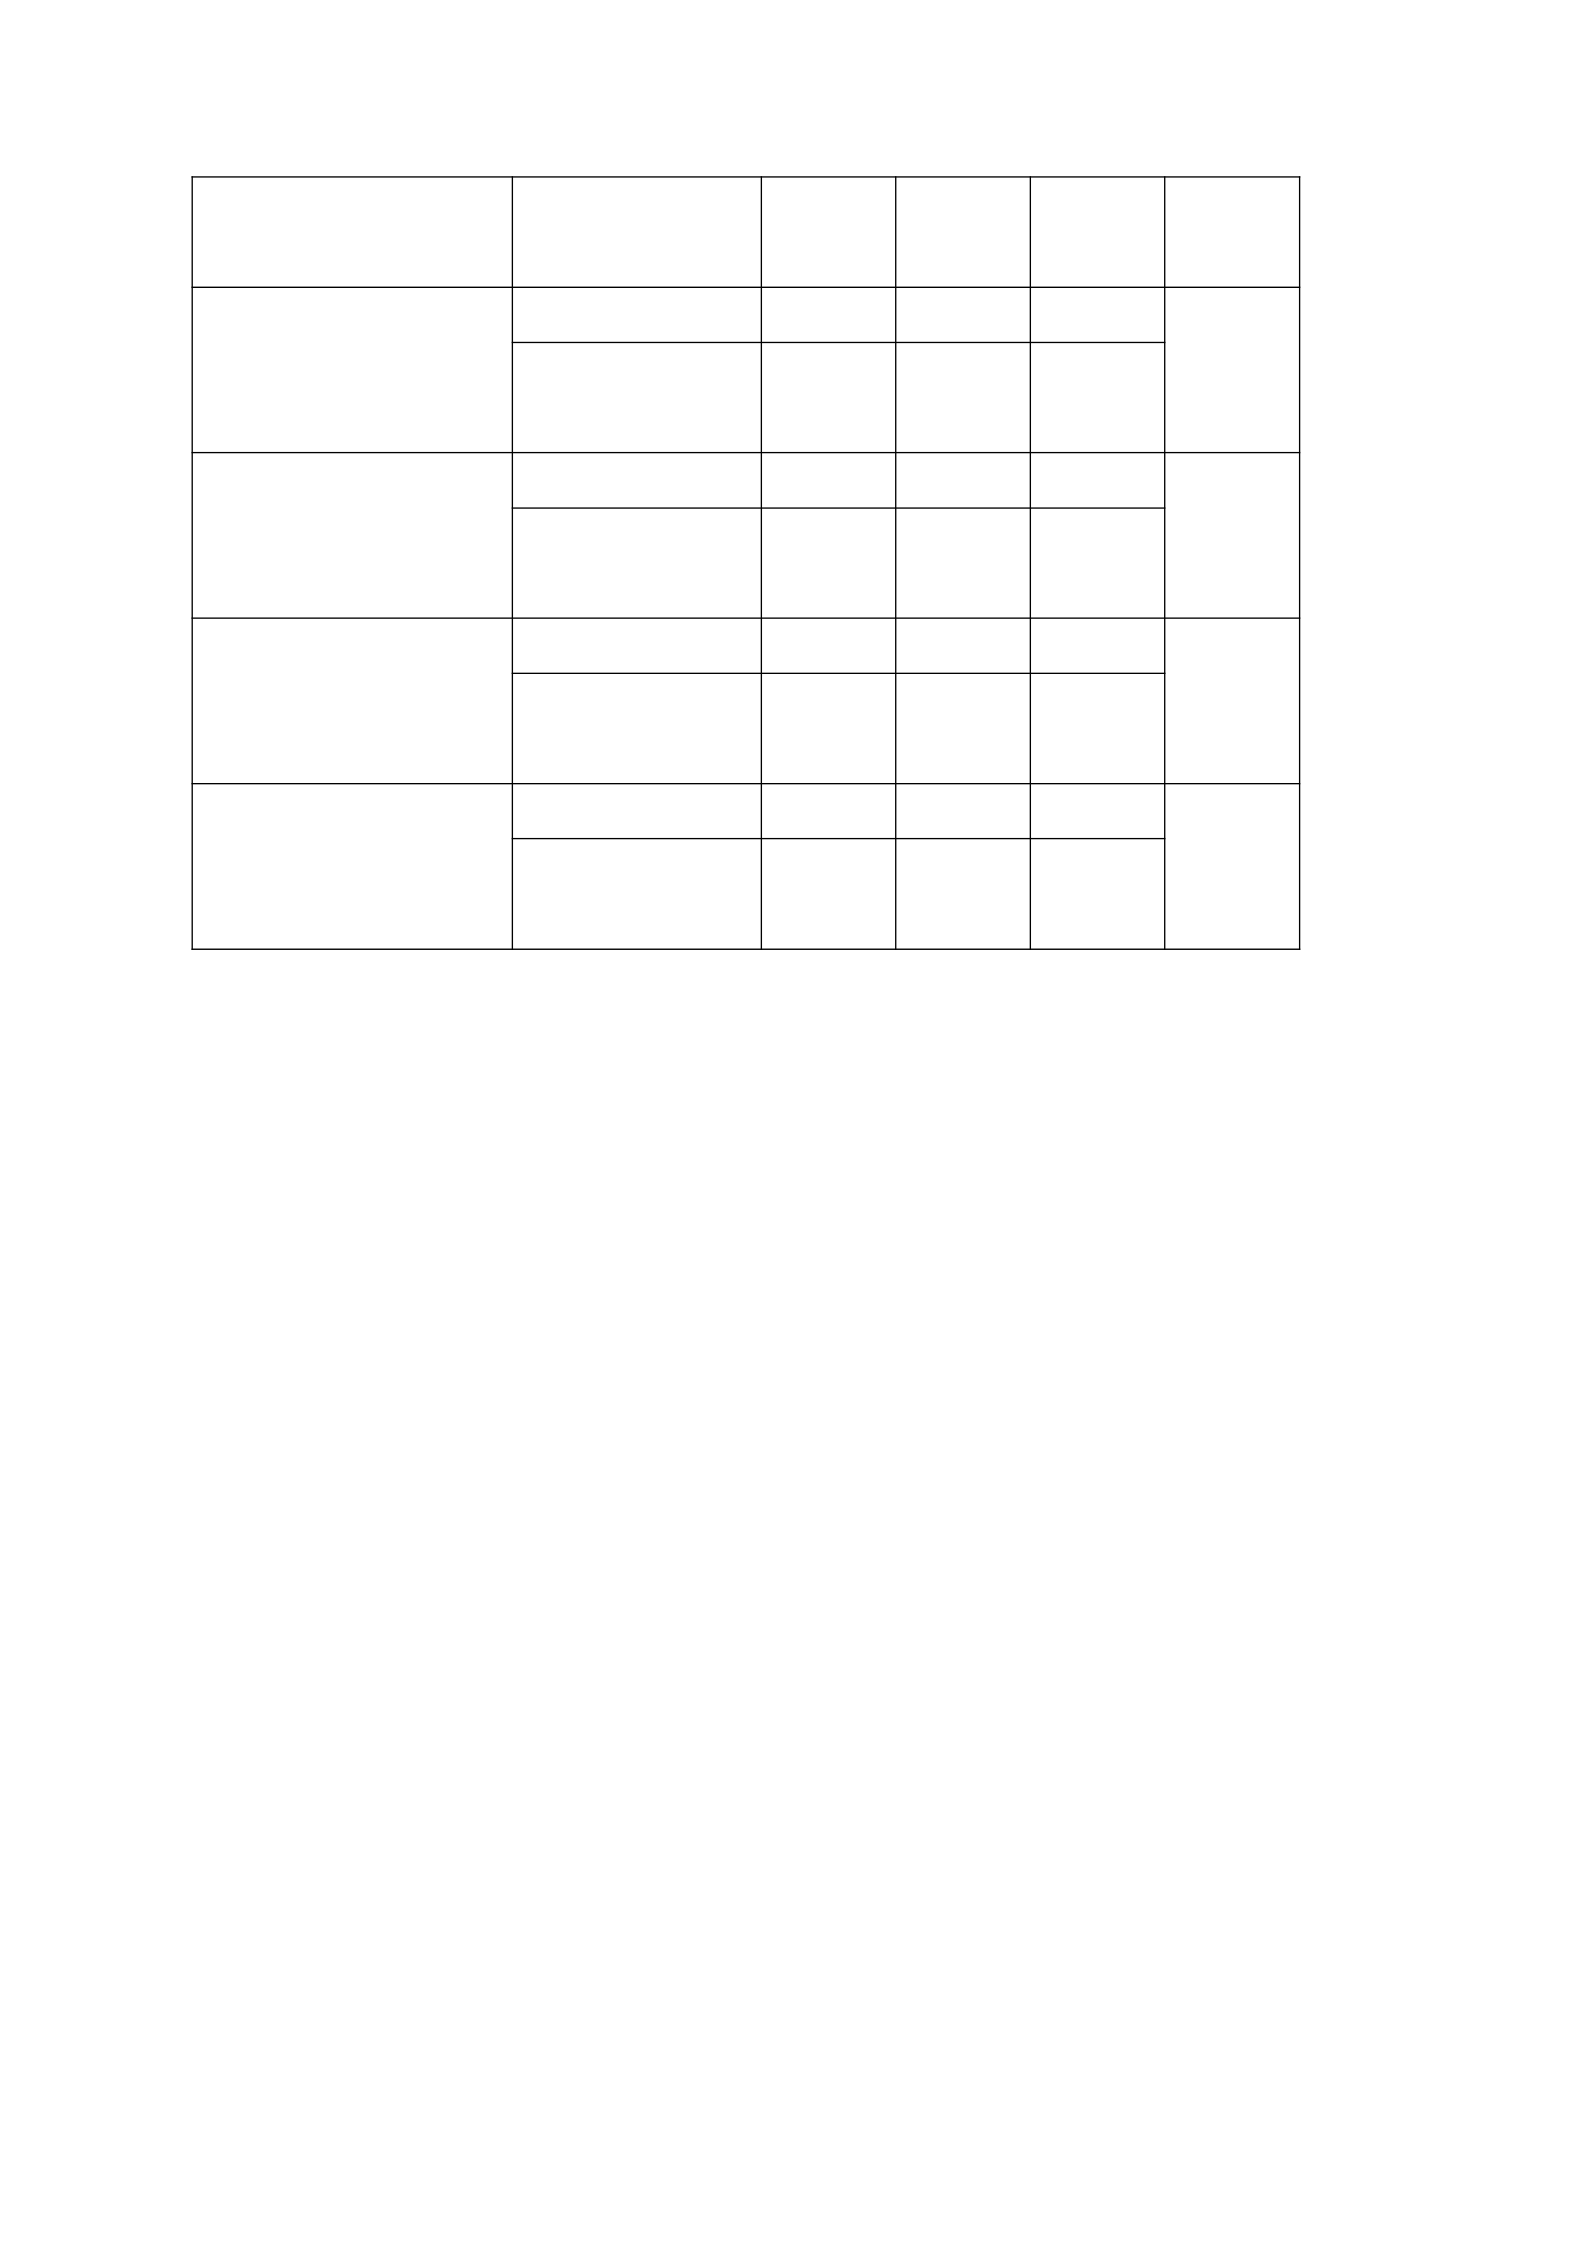
7 (85.7%) non-hypertensive patients had mild hearing loss while 1 had severe SNHL.
Table: patients with hearing loss in both cases and controls
Arm
Case Control
n
% N %
p-value
Hearing loss defined by
above 25 decibels
Hearing loss 13 25.5 7 13.7 0.135
No hearing
loss 38 74.5 44 86.3
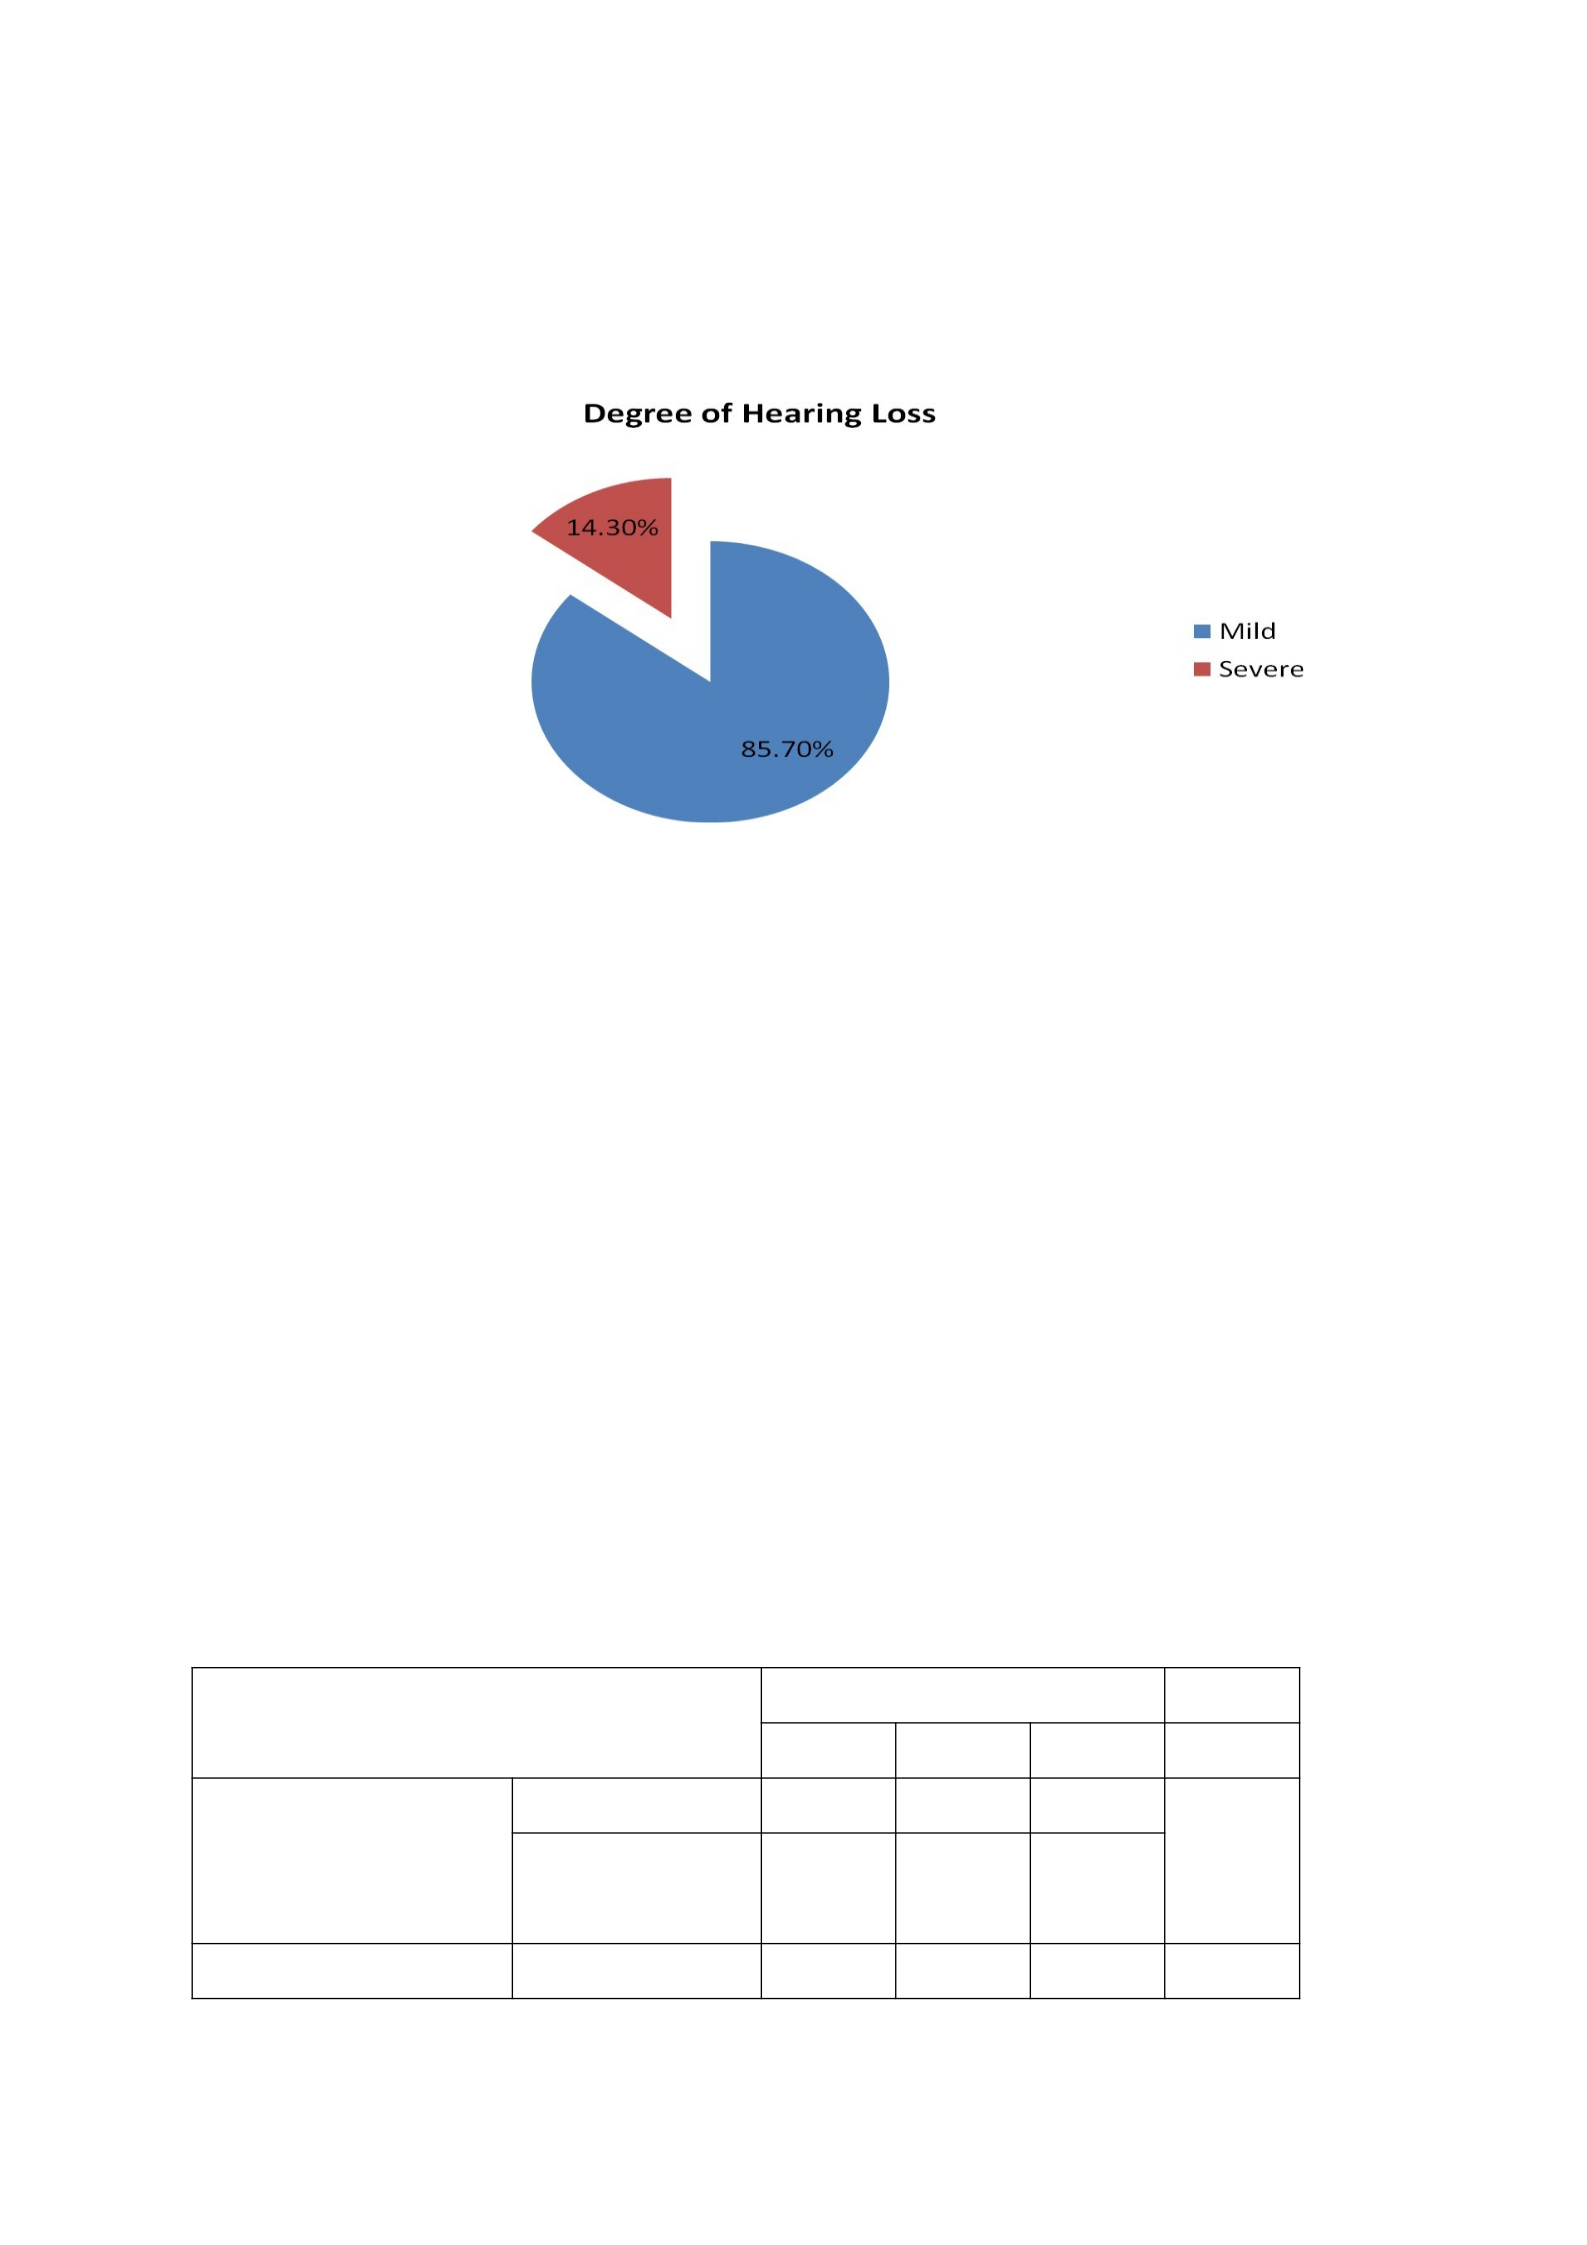
Figure: Pie chart showing degree of hearing loss distribution among cases
Figure: showing degree of hearing loss distribution among controls
Pattern of hearing loss
The configuration of hearing loss was divided into low, mid and high frequency hearing loss.
For the low frequency the mean was 20.3 dB on the right ear and 17.6 dB on the left for cases.
The low freguency for the controls was 17.1 dB on the right ear and 15.7 dB on the left. There
was an increase in the mid and high frequency with the right ear having 26 dB and the left ear
23.3 dB in the cases. The right ear had 24.9 dB and the left 23.2 dB in the control arm. The P-
values ranged from 0.222-0.912 and were not statistically significant.
Table: pattern of hearing loss
Arm
Case Control Total p-value
PTA Right Ear 250-
500
Mean 20.3 17.1 18.7 0.222
Standard
Deviation 15.8 9.6 13.1
Mean 17.6 15.7 16.6 0.251
PTA Left Ear 250-500
Standard
Deviation 9.2 7.5 8.4
PTA Right Ear 1000-
2000
Mean 18.2 15.5 16.9 0.324
Standard
Deviation 17.2 9.7 14.0
PTA Left Ear 1000-
2000
Mean 15.2 14.6 14.9 0.748
Standard
Deviation 10.9 7.2 9.2
PTA Right Ear 4000-
8000
Mean 26.0 23.8 24.9 0.489
Standard
Deviation 18.7 12.8 16.0
PTA Left Ear 4000-
8000
Mean 23.3 23.0 23.2 0.912
Standard
Deviation 15.7 10.7 13.4
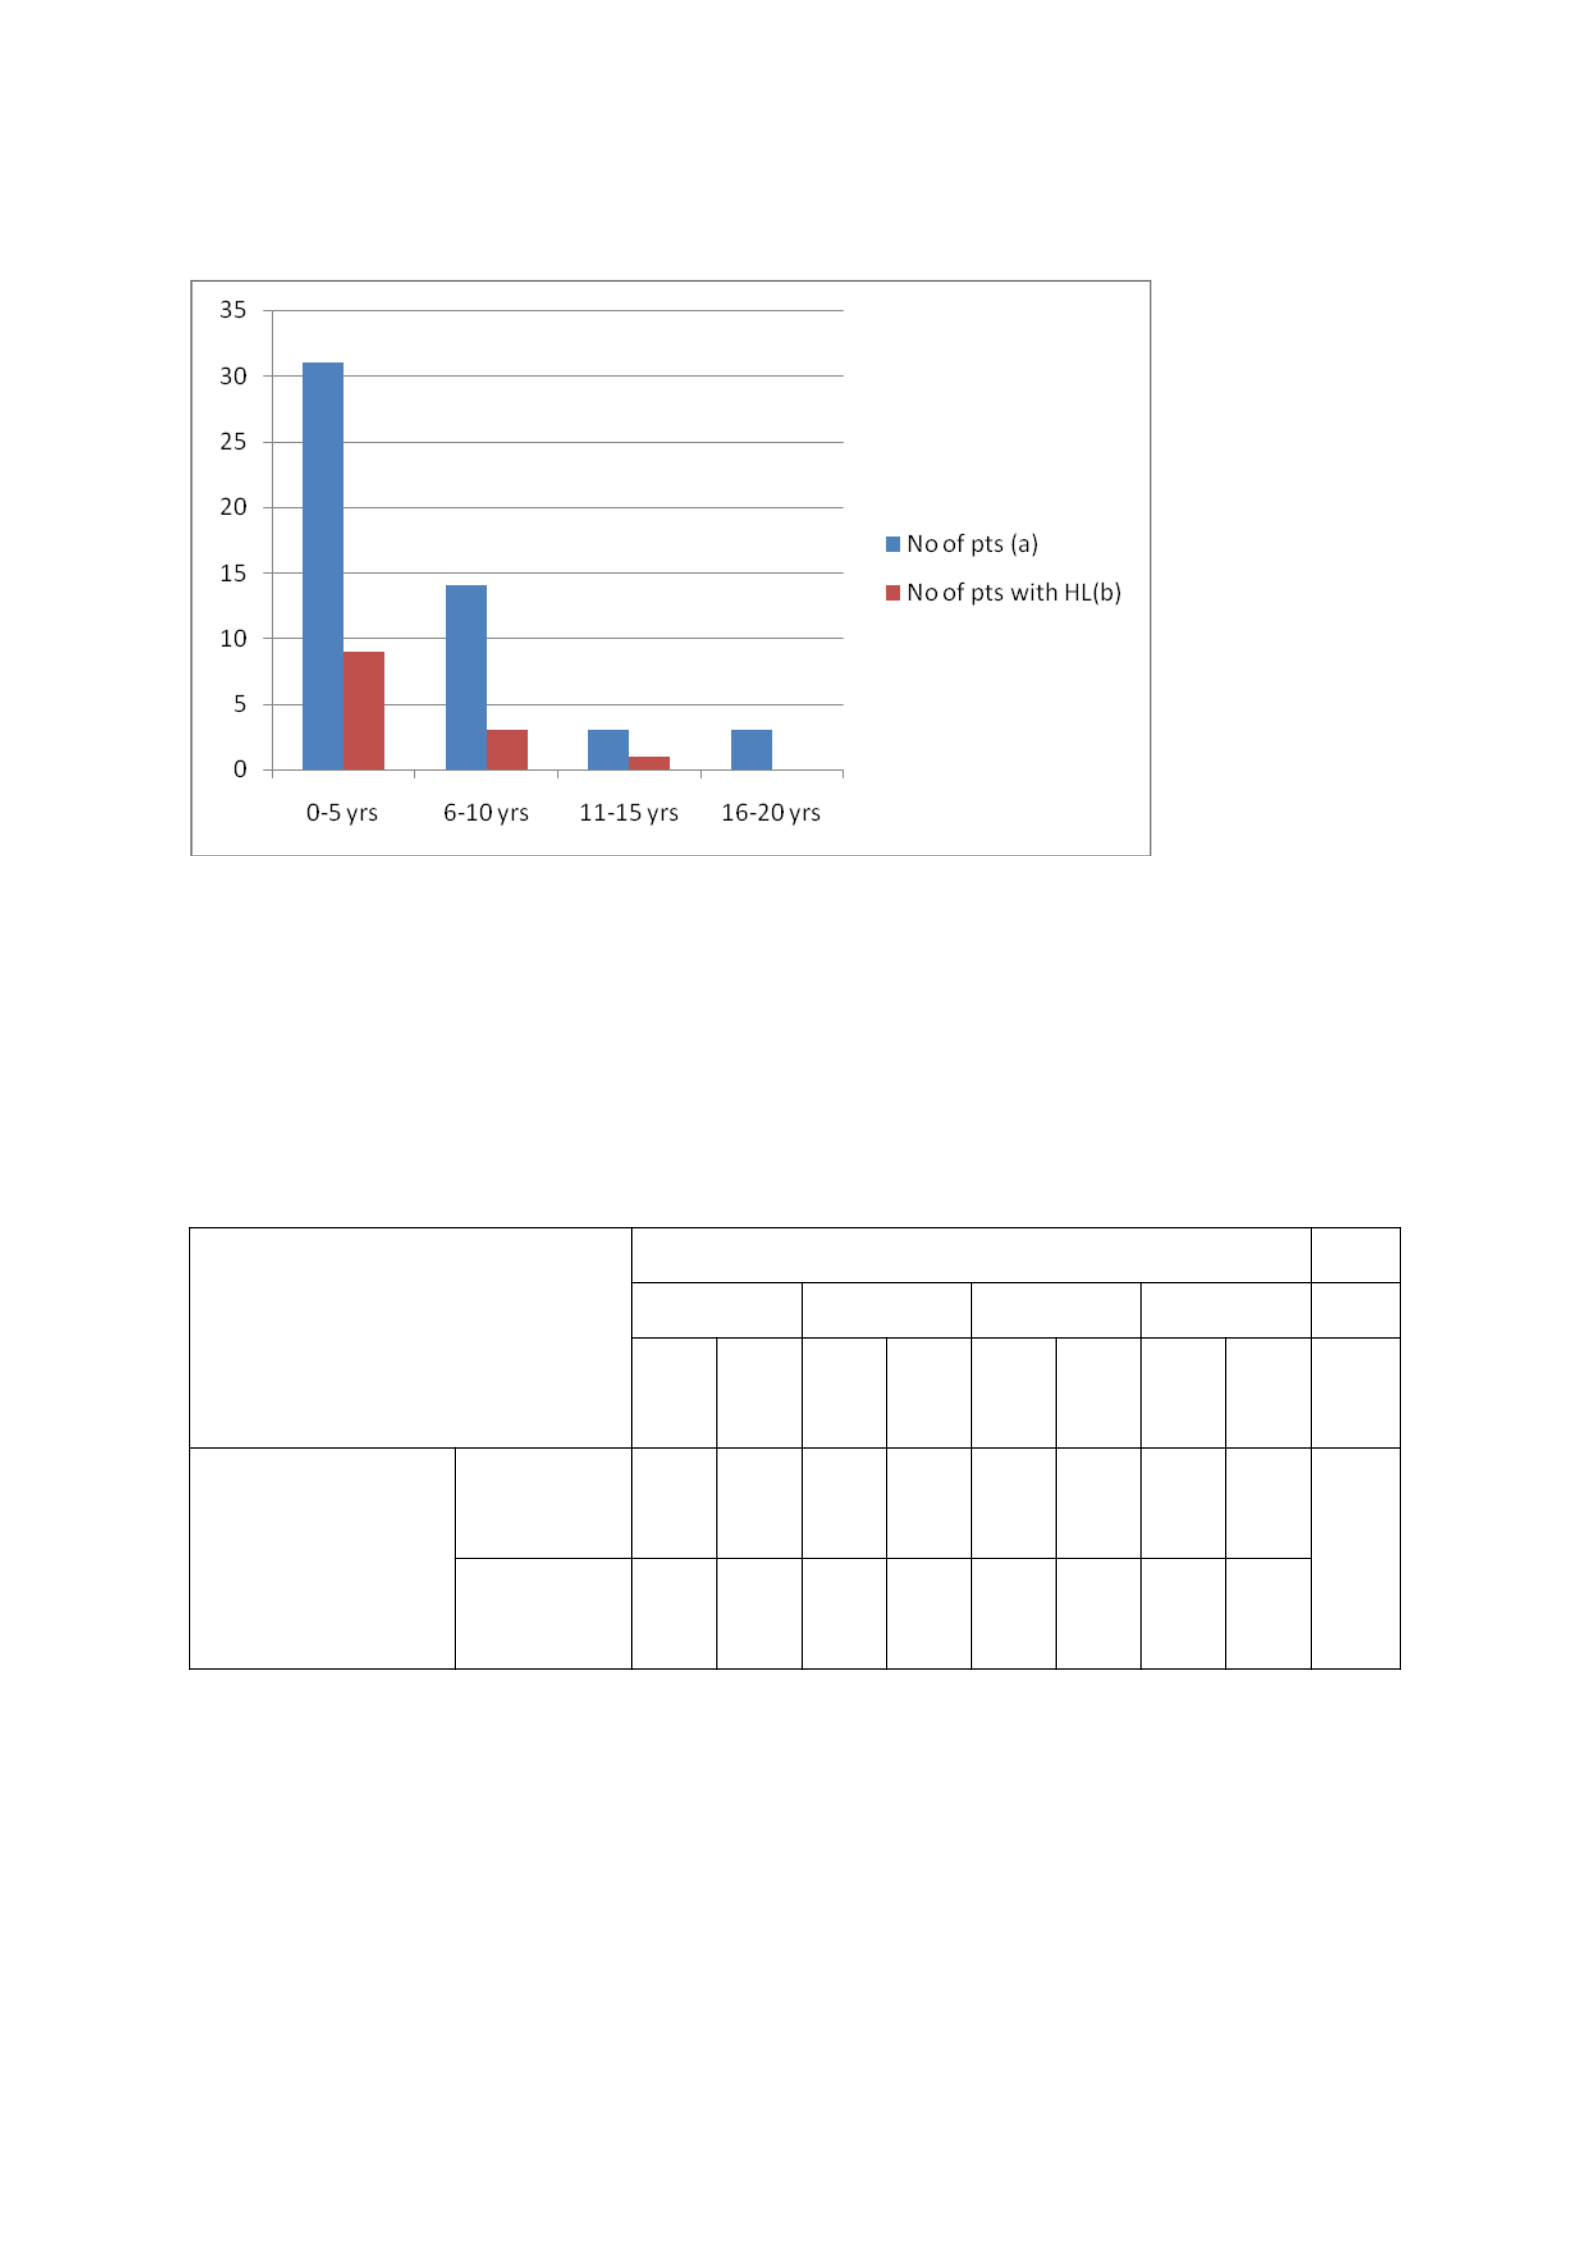
Figure: Duration of treatment and number of patients with hearing loss
Nine (29%) of the patients treated for ≤ 5 years had hearing loss while 1 out of the 3 (33.3%)
patients treated for 11-15 years had hearing loss.
Table: Grade of hypertension and hearing loss
BP grade
Normal Grade 1 Grade 2 Grade 3
N % N % N % N %
p-
value
Hearing loss
defined by above
25 decibels
Hearing
loss
6 33.3 4 18.2 3 27.3 0 .0 0.543
No hearing
loss
12 66.7 18 81.8 8 72.7 0 .0
Four (18.2%) of patients with grade 1 and 3 (27.3%) of patients with grade 2 hypertension
had hearing loss. This was not statistically significant (p value=0.543).
Table: Pearson correlation between age and hearing loss
a. Arm = Case
Age PTA Right Ear PTA Left Ear
Pearson Correlation 1 .078 .289*
Age Sig. (2-tailed) .587 .040
N
51 51
PTA
Right Ear
Pearson Correlation 1 .473**
Sig. (2-tailed) .000
N
51
Pearson Correlation 1
PTA Left
Ear Sig. (2-tailed)
N
51
*. Correlation is significant at the 0.05 level (2-tailed).
**. Correlation is significant at the 0.01 level (2-tailed).
a. Arm = Control
Age PTA Right Ear PTA Left Ear
Pearson
Correlation 1 .206 .612**
Age Sig. (2-tailed) .146 .000
N
51 51
PTA
Right Ear
Pearson
Correlation 1 .465**
Sig. (2-tailed) .001
N
51
PTA
Left Ear
Pearson
Correlation 1
Sig. (2-tailed)
N
51
**. Correlation is significant at the 0.01 level (2-tailed).

DISCUSSION
Hearing loss which has multifactorial causation is currently a public health concern. Several
studies in developed countries have been conducted to find out whether hypertension is one of
the risk factors . The results have been contradictory with some showing positive correlation
(4,40,45,48 ) while others have shown no association between hearing loss and hypertension
(42,44). With that in mind this study was conducted to ascertain whether hypertension is a
risk factor for hearing loss in our set up where such data is not available.
This hospital based case control study recruited 38 female patients (74.5%) who were
hypertensive and on treatment as cases & 38 non-hypertensive as controls. Thirteen
hypertensive males (25.5%) were picked as cases and 13 non hypertensive as controls. The
cases and controls were gender and age matched within 3 years. The age (p-value=0.174) and
gender (p-value=1) differences were not statistically significant. However the studies by Chen
et al (3) with 100% and Agarwal et al (40) with 65.8% had high numbers of male subjects.
This may account for some differences in the results as males are more predisposed to hearing
loss as shown by Pearson et al (49) and Dubno et al (50). Some studies have also used older
populations (3, 43). The prevalence of hearing loss is known to increase with aging (50) hence
this may account for the difference in results with this studies.
The mean duration of treatment was 5.78 years with the longest treatment period been 20
years. This compared to the study by Agarwal et al (40) with a mean ranging from 3.73 years
for grade 1, 5.46 years for grade 2 and 9.05 years for grade three. In our study, the duration of
treatment had a slight influence on hearing loss with 29% of those in the 0-5 years category
and 33.3% in the 11-15years having hearing loss but it was not statistically significant. This
was not in keeping with Agarwal et al (40) who showed a strong correlation between duration
of hypertension and hearing loss. The group with a mean duration of 3.7 years had 36.7%

hearing loss while the group with a mean of 9 years had hearing loss in 54.2%. The longer
duration of hypertension is postulated to increase the risk of ischemic damage to the cochlea
through vascular changes (48).
Twenty of the hypertensive patients (39.2%) had tinnitus while only two of the controls had
tinnitus. This was statistically significant with a p-value =<0.0001. This is slightly lower than
in Mondelli et al (45) study where 43.7% of the hypertensive patients had tinnitus.
Hypertension as a risk factor for tinnitus has been demonstrated in other studies (51,52, 53).
This is due to its effect as a high output state (pulsatile tinnitus), effects of antihypertensive
medication or in relation to hearing loss. There was also a correlation between tinnitus and
hearing loss as 5 of the 20 cases (25%) with tinnitus had hearing loss while the 2 (100%) in
control arm had hearing loss.
The mean blood pressure for cases was 146/85mmHg and for controls was 125/79mmHg.
Hypertension has been associated with hearing loss (4,48) which is thought to occur due to
microcirculatory insufficiency with prevalence ranging between 7.3% to 59.2%. In our study
patients with hypertension were at higher risk of hearing loss 25.5% as compared to controls
(13.7%). However this was not statistically significant at a p value of 0.135. The low
prevalence may be explained by the fact that in our study we recruited both the well
controlled hypertensives (35.3%) and the uncontrolled hypertensives. The mean blood
pressure was also relatively low. The percentage of hypertensive patients on treatment with
well controlled BP is similar to the results of JNC7 (21). Our findings are similar to other
studies (42,44) which have shown a weak link between high blood pressure and hearing loss.
Its postulated that the autoregulatory mechanisms of inner ear may be able to buffer it from
effects of systemic vascular disorders. The grade of hypertension was also found not to have a
major influence on hearing loss (p-value=0.543) . The grade of hypertension was one of this

study’s limitation given the fact that blood pressure fluctuates and this could account
for this findings.
The pure tone audiometry thresholds were increased in all the frequencies slightly
more for cases (hypertensives) as compared to the controls which indicates a
possible effect of high blood pressure on hearing loss. The p values ranged from
0.184 to 0.879 and were statistically not significant. The increase in PTA thresholds
is similar to other studies (3,41,54).
The pattern of hearing loss demonstrated a mild sloping configuration with all
frequencies affected more in the hypertensive patients than in the controls.
Hypertensive micro angiopathy has been postulated to affect cochlear
microcirculation in all turns hence why all the frequencies are affected. This was
similar to other research (55, 56) findings. Some other studies found that low and
mid frequencies were more affected Marchiori et al (4). The explanation for that was
that the cochlea apex was more affected during ischemic episodes. This is
questionable since the inner ear has possible micro circulation autoregulation and
vascular anastomosis.

