


Motivation and behavior change in promoting physical activities
Motivation has been defined as the ‘internal and/or external forces that
produce the initiation, direction, intensity and persistence of behaviour’ (Vallerand et
al., 2004, pg. 428). Motivation plays a central role in determining all aspects of
human behaviour, and differs greatly from one individual to another, as well as
differing within contexts. Promoting PA among MHSU who face a lack of
motivation towards engagement can be challenging (Teixeira et al., 2012).
Additionally, due to such differences between individuals and within contexts, there
is a need to understand motivational processes involved in certain behaviours. For
example, motivation towards PA engagement of MHSU, and the motivation behind
peer volunteering within a community PA programme. Motivation and processes of
behaviour change are best understood within theoretical frameworks which can be
employed to explain processes of change in many life contexts.
Theoretical approaches to motivation and behavior change
It is important to establish a theoretical foundation when conducting research
to consider a) the underlying motivational processes of individuals who volunteer
peer support
to MHSU; and b) to enhance the PA levels of MHSU through a community PA
programme. There are several theories that have been developed to help aid the
understanding of the underlying processes of human behaviour. However, questions
can be asked when considering the utility of, and application of theories to, the
current PhD research. Firstly, a highly utilised theory to explain health behaviour
change is the transtheoretical model of behaviour change (TTM; DiClemente &
Prochaska, 1983) which considers an individual’s readiness to change and proposes
that this occurs through progression of five stages; Precontemplation (no intention to
change and a lack of awareness for the need to change); Contemplation (aware that
there is an issues and is considering change); Preparation (action planning and
whereby an individual begins to make small changes); Action (individual is actively
trying to change by carrying out new behaviours); and Maintenance (new behaviours
have been established and an individual is trying to sustain changes). While the stages
of change are useful in explaining when changes in cognition, emotion, and behaviour

take place, the processes of change help to explain how those changes occur
(Prochaska, Redding, & Kerry, 2008). These ten covert and overt processes, which
can be divided into two groups of cognitive and affective experiential processes and
behavioural processes, need to be implemented to successfully progress through the
stages of change and attain the desired behaviour change (Prochaska et al., 2008).
Theorists suggested that the stages of change were discrete and independent
of each other (DiClemente & Prochaska, 1983). However, limited evidence has been
found for the effectiveness of TTM (Bridle et al., 2005) which, as a theory, fails to
consider the role of individuals’ unconscious processes such as reward and
punishment (Bridle et al., 2005). A further criticism is the lack of evidence for
discrete stages of change or for the model’s assumption that people make coherent
plans to transition smoothly through stages (Bridle et al., 2005). NICE (2014)
expressed concern that this theory is still being used as a theory of behaviour change
even though it does not accurately explain or predict behaviour change.
When considering suitability for this PhD, TTM is unsuitable because MHSU may
not smoothly transition through stages in the order like the model suggests. For
example, individuals may experience a relapse in their mental health during the
programme, however, may return back to PA via the contemplation or action stage
rather than the initial precontemplation stage. Therefore, a theory which explains
changes in behaviour is required. Additionally, TTM neglects the social determinants
of an individual that such factors might impact on health-related behaviour such as
PA (Taylor et al., 2006). Consequently, a theory which acknowledges the influence
of the social contextual environment on health behaviours is warranted.
Secondly, a further theory of behaviour change that fails to acknowledge the
role of unconscious processes is the theory of planned behaviour (TPB; Ajzen, 1985)
which states that intention is the best predictor of behaviour, developed after a person
has evaluated a change in behaviour and its outcomes. Evaluation is influenced by
attitudes towards a behaviour such as PA (positive, negative or neutral) and therefore
affect engagement (Azjen, 1985). Other influences on evaluation include subjective
norms (an individual’s perception of what they think other individuals do
comparatively), with higher conformity to social norms if a person feels they arise

from individuals they respect, and finally perceived behavioural control (how easy or
difficult a person believes it will be to change a particular behaviour) with beliefs
being generated from past experience and health beliefs, and developed by internal
and external factors (Azjen, 1985).
Results from a systematic review found support for the central assumption that
intention is a strong predictor of behaviour (Barley & Lawson, 2016; McEachan,
Conner, Taylor, & Lawton, 2011). However, greater support was found for the
model’s ability to explain intention to change rather than for its ability to predict
actual behaviour (McEachan et al., 2011). A major criticism of TPB highlights the
theory’s exclusive focus on rational reasoning, excluding the role of emotions beyond
anticipated affective outcomes (Sniehotta, Presseau, & Araújo-Soares, 2015). MHSU
experience heightened emotion which is the foundation of their mental illness.
Emotion, therefore, plays a key role in establishing motivation towards PA behaviour.
TPB relies on individual cognitions and fails to explain how a social environment can
facilitate engagement in health behaviours, such as PA, further highlighting this
theory’s unsuitability for this PhD.
Self-determination theory of human motivation
Having discussed two popular behaviour change theories, it is apparent that
many PA programmes still attempt to achieve outcomes such as motivation towards
behaviour change and positive psychological wellbeing without consideration of
emotion and underlying processes (Ng et al., 2012). Self-determination theory
provides a theoretical framework that has been successfully used within the health
promotion and behaviour change domain (Ng et al., 2012). Self-determination theory
(SDT; Deci & Ryan, 2000) is a macro theory of human motivation which is
concerned with individuals’ behavioural tendencies, personality development, self-
regulation, psychological needs and the impact of social environments on affect,
behaviour and wellbeing.
SDT comprises six mini-theories (Deci & Ryan, 2000). These are the
cognitive evaluation theory (CET; concerning intrinsic motivation), organismic
integration theory (OIT; addressing the topic of extrinsic motivation), causality
orientations theory (COT; describes individual differences in individuals’ tendencies
to regulate behaviour), basic psychological needs theory (BPNT; elaborates the
concept of basic psychological needs and their relation to psychological health), goal
contents theory (GTT; the distinction between intrinsic and extrinsic goals), and
relationships motivation theory (RMT; the development and maintenance of close
relationships and the links to basic psychological need satisfaction).
Contemporary theories of motivation have treated motivation as a unitary
concept with a focus on the overall amount of motivation an individual has towards a
particular behaviour. However, SDT differentiates types of motivation and states that
this is of greater importance in predicting outcomes such as psychological health and
wellbeing in comparison to the total amount of motivation (Ryan et al., 2008). The
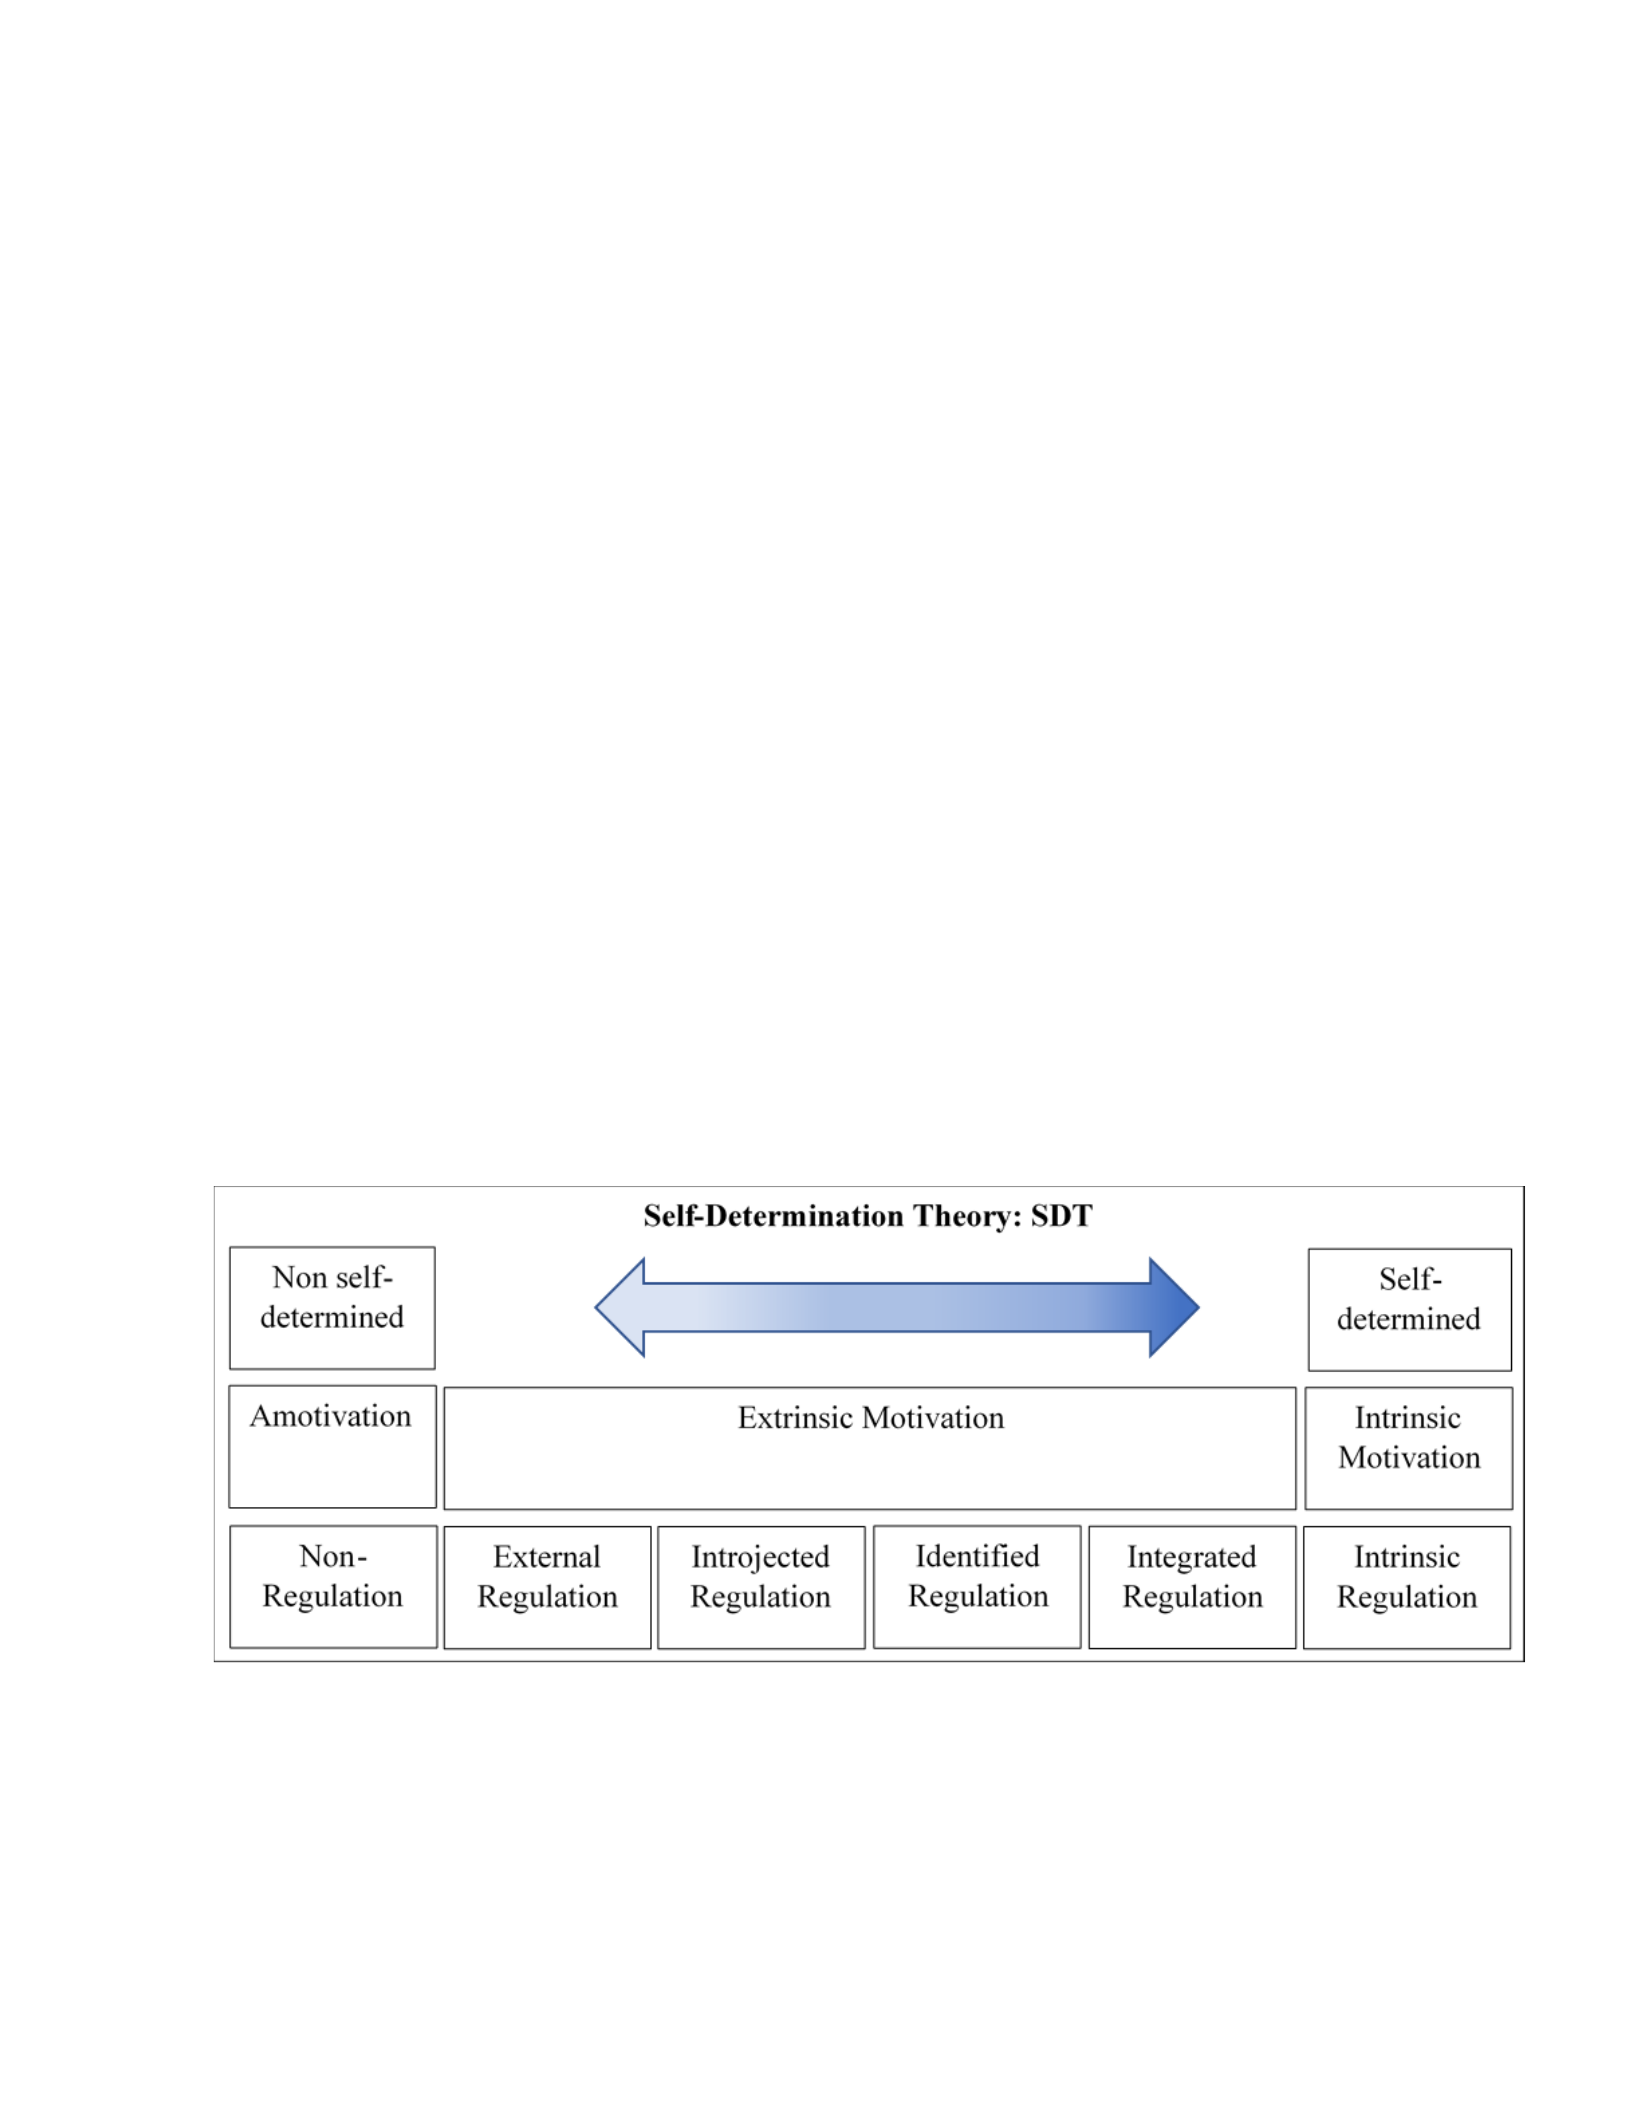
different types of motivation proposed by theorists of SDT are on a continuum
between autonomous (intrinsic or extrinsic forms whereby individuals identify with
an activity’s value and integrate it into their sense of self) and controlled (external
regulation in which an individual’s behaviour is a function of external contingencies
of reward/punishment and introjected regulation meaning the behaviour becomes
partially internalised and is energised by factors such as avoidance of shame,
approval motives or ego involvement). Figure 1.1 outlines the continuum of
motivation regulations.
Figure 1.1. A diagram of the Self-determination theory motivation regulation
continuum (Deci & Ryan, 2000).
A systematic review produced consistent support for a positive relationship
between autonomous forms of motivation and exercise, with intrinsic motivation

being more predictive of long-term exercise adherence (Ng, Ntoumanis, Thøgersen-
Ntoumani, Stott, &
Hindle, 2013; Teixeira, Carraça, Markland, Silva, & Ryan, 2012). Moreover,
autonomous motivation leads to individuals experiencing volition of their actions
compared to controlled motivation where an individual experiences pressure to think,
feel or behave in a particular way (Ryan et al., 2008). Despite the suggestion that both
forms of motivation energise and direct an individual’s behaviour, autonomous
motivation leads to greater psychological health (Knittle et al., 2018).
Self-determination theorists also propose that all individuals strive to satisfy
three psychological needs to facilitate motivation towards behavioural adoption,
maintenance and adherence within a particular context (Ryan et al., 2008). This
concept provides a means of understanding how various social forces and
interpersonal environments affect autonomous versus controlled motivation (Ryan et
al., 2008). Firstly, the need for autonomy refers to feelings of volition and free will in
the sense that the individual is in control of their behaviours. Secondly, individuals
strive to satisfy the need to feel competent or effective in carrying out behaviours and
handling situational demands. Thirdly, individuals have a need to feel related and
connected, further feeling accepted by significant others in the given context.
Perceptions of significant others, therefore, can be developed on the basis of need
fulfilment and the extent to which one’s basic psychological needs of autonomy,
competence and relatedness are satisfied (Ryan et al., 2008). Greater fulfilment of
these needs has been found to be associated with better mental and physical health,
and healthier behaviour (Ng et al., 2012).
SDT’s emphasis on supporting basic psychological needs is consistent with
general principles of patient care, making its practical utility in clinical and
healthcare contexts paramount (Patrick & Williams, 2012). Additionally, this theory
accounts for how behaviour is energised as well as the direction of behaviour itself in
comparison to other theories, such as TTM and TPB, which fail to do this.
One of the key assumptions of the SDT perspective is that need fulfilment
arises out of certain optimal social contexts such as need supportive environments
whereby these interactions take place (Deci & Ryan, 2000). Self-determination

theorists (Deci & Ryan, 2008) propose that individuals providing autonomy support
within a context such as PA would offer choice in activities, acknowledge an
individual’s perspective and seek their input within the given context, as well as
provide meaningful information and rationale to encourage behaviours and support
personal choice regarding behaviour change (Duda et al., 2014). However, it has
been argued that too much emphasis has been placed on supporting an individual’s
need for autonomy within a given social context, failing to consider the other
two psychological needs of competence and relatedness within need supportive
environments (Rouse et al., 2011).
This has developed into new SDT-based conceptualisations of the social
environment which have expanded to include support for psychological needs of
competence and relatedness, as opposed to focusing solely on autonomy support
(Rouse, Duda, Ntoumanis, Jolly, & Williams, 2016). Current research is interested in
the degree to which social environments are characterised by structure (supporting
competence) and involvement (concerns relatedness) alongside levels of autonomy
support (Rouse et al., 2016). SDT considers individuals in the context of the
combined influence of psychological factors and their surrounding social
environment (Omoto & Packard, 2016; Solomon, 2004). It is critical to identify the
most effective methods of creating need supportive environments for MHSU by
incorporating peer support to satisfy all three psychological needs within the PA
environment.
A ‘significant other’ (traditionally thought of as a respected person in a
position of authority) can positively impact motivation towards behavioural adoption,
maintenance and adherence towards physical activity by taking on need supportive
behaviours (Duda et al., 2014). This macro-theory of motivation is therefore relevant
to the work carried out as part of this thesis as it can be used to explain how the socio-
contextual environment can influence motivation (Rouse et al., 2011). Research in the
field of PA has investigated autonomy supportive environments created by exercise
professionals. However, much less research has examined support provided from less
authoritative important others such as family and peers (Kinnafick, Thøgersen-
Ntoumani, & Duda, 2014; Ng et al., 2012; Ntoumanis, Quested, Reeve, & Cheon,

2018).
SDT will be used in the current body of work to shed further light on the
psychological processes underlying motivation towards behaviour change, PA
participation and maintenance, whilst exploring the concept of peers as ‘significant
others’ providing need support to MHSU within a community PA context. When
identifying the most effective ways of facilitating need supportive environments, the
majority of studies have considered face to face provision of need support from
significant others such as exercise providers (Edmunds, Ntoumanis, & Duda, 2008;
Rouse, Ntoumanis, Duda, Jolly, & Williams, 2011). However, little research has
considered a ‘significant other’ in the role of a peer, and there is a paucity of research
that has considered different modes of need support delivery, for example through
social media, online forums or an online community (Naslund, Aschbrenner, Marsch,
& Bartels, 2016). This PhD will consider the role of peer support delivery face-to-face
and via an online communication platform on motivation towards PA engagement.
References
Ainsworth, B. E., Caspersen, C. J., Matthews, C. E., Mâsse, L. C., Baranowski, T., & Zhu,
W. (2016). Recommendations to Improve the Accuracy of Estimates of Physical
Activity Derived from Self Report. Journal of Physical Activity and Health.
https://doi.org/10.1123/jpah.9.s1.s76
Aknin, L. B., Dunn, E. W., Sandstrom, G. M., & Norton, M. I. (2013). Does social
connection turn good deeds into good feelings? On the value of putting the “social” in
prosocial spending. International Journal of Happiness and Development.
https://doi.org/10.1504/ijhd.2013.055643
Ali, K., Farrer, L., Gulliver, A., & Griffiths, K. M. (2015). Online Peer-to-Peer Support for
Young People With Mental Health Problems: A Systematic Review. JMIR Mental
Health, 2(2), e19. https://doi.org/10.2196/mental.4418
Allen, J., Balfour, R., Bell, R., & Marmot, M. (2014). Social determinants of mental health.
International Review of Psychiatry, 26(4), 392–
407.
https://doi.org/10.3109/09540261.2014.928270
Andersen, S. M., & Berk, M. S. (1998). Transference in everyday experience:
Implications of experimental research for relevant clinical phenomena. Review of
General Psychology. https://doi.org/10.1037/1089-2680.2.1.81
Anderson, K., Laxhman, N., & Priebe, S. (2015). Can mental health interventions change

social networks? A systematic review. BMC Psychiatry, 15(1).
https://doi.org/10.1186/s12888- 015-0684-6
Andrew, S., & Halcomb, E. J. (2006). Mixed methods research is an effective method of
enquiry for community health research. Contemporary Nurse.
https://doi.org/10.5172/conu.2006.23.2.145
Ashida, S., & Heaney, C. A. (2008). Differential associations of social support and
social connectedness with structural features of social networks and the health
status of older adults. Journal of Aging and Health.
https://doi.org/10.1177/0898264308324626
Bellamy, C., Schmutte, T., & Davidson, L. (2017). An update on the growing evidence base
for peer support. Mental Health and Social Inclusion. https://doi.org/10.1108/MHSI-
03-2017- 0014
Berger, M., Wagner, T. H., & Baker, L. C. (2005). Internet use and stigmatized illness.
Social Science and Medicine. https://doi.org/10.1016/j.socscimed.2005.03.025
Berry, K., Rana, R., Lockwood, A., Fletcher, L., & Pratt, D. (2019). Factors associated
with inattentive responding in online survey research. Personality and Individual
Differences. https://doi.org/10.1016/j.paid.2019.05.043
Bidee, J., Vantilborgh, T., Pepermans, R., Huybrechts, G., Willems, J., Jegers, M., & Hofmans,
J. (2013). Autonomous Motivation Stimulates Volunteers’ Work Effort: A
Self- Determination Theory Approach to Volunteerism. Voluntas, 24(1), 32–
47. https://doi.org/10.1007/s11266-012-9269-x
Bledin, K., Loat, M., Caffrey, A., Evans, K. B., Taylor, B., & Nitsun, M. (2016). ‘Most
Important Events’ and Therapeutic Factors: An Evaluation of Inpatient Groups for
Peoplewith Severe and Enduring Mental Health Difficulties. Group Analysis.
https://doi.org/10.1177/0533316416675442
Bopp, M., & Fallon, E. (2008). Community-based interventions to promote increased
physical activity: A primer. Applied Health Economics and Health Policy, 6(4), 173–
187. https://doi.org/10.2165/00148365-200806040-00001
Bowling, N. A., Huang, J. L., Bragg, C. B., Khazon, S., Liu, M., & Blackmore, C. E.
(2016). who cares and who is careless? Insufficient effort responding as a reflection of
respondent personality. Journal of Personality and Social Psychology, 111(2), 218–
229. https://doi.org/10.1037/pspp0000085
Brand, T., Pischke, C. R., Steenbock, B., Schoenbach, J., Poettgen, S., Samkange-Zeeb, F.,
& Zeeb, H. (2014). What works in community-based interventions promoting physical
activity and healthy eating? A review of reviews. International Journal of
Environmental Research and Public Health. https://doi.org/10.3390/ijerph110605866
Braun, V., & Clarke, V. (2006). Using thematic analysis in psychology. Using
Qualitative Research in Psychology, 3, 77–101. https://doi.org/The publisher’s
URL is: http://dx.doi.org/10.1191/1478088706qp063oa

Braun, V., & Clarke, V. (2006). Using thematic analysis in psychology. Qualitative
Research in Psychology, 3(May 2015), 77–101.
https://doi.org/10.1191/1478088706qp063oa
Braun, V., & Clarke, V. (2014). What can “thematic analysis” offer health and wellbeing
researchers? International Journal of Qualitative Studies on Health and Well-
Being, 9. https://doi.org/10.3402/qhw.v9.26152
Braun, V., & Clarke, V. (2019). Reflecting on reflexive thematic analysis. Qualitative
Research in Sport, Exercise and Health.
https://doi.org/10.1080/2159676X.2019.1628806
Bryant, W., Tibbs, A., & Clark, J. (2011). Visualising a safe space: The perspective of
people using mental health day services. Disability and Society.
https://doi.org/10.1080/09687599.2011.589194
Burr, J. A., Han, S. H., & Tavares, J. L. (2016). Volunteering and Cardiovascular Disease
Risk: Does Helping Others Get “under the Skin?” Gerontologist, 56(5), 937–947.
https://doi.org/10.1093/geront/gnv032
Burton, E., Farrier, K., Hill, K. D., Codde, J., Airey, P., & Hill, A. M. (2018). Effectiveness
of peers in delivering programs or motivating older people to increase their
participation in physical activity: Systematic review and meta-analysis. Journal of
Sports Sciences, 36(6), 666–678. https://doi.org/10.1080/02640414.2017.1329549
Carey, E. C., & Weissman, D. E. (2010). Understanding and finding mentorship: A review
for junior faculty. Journal of Palliative Medicine.
https://doi.org/10.1089/jpm.2010.0091
Carless, D., & Douglas, K. (2008a). Social support for and through exercise and sport in a
sample of men with serious mental illness. Issues in Mental Health Nursing, 29(11),
1179– 1199. https://doi.org/10.1080/01612840802370640
Carless, D., & Douglas, K. (2008b). The contribution of exercise and sport to mental
health promotion in serious mental illness: An interpretive project. International
Journal of Mental Health Promotion, 10(4), 5–12.
https://doi.org/10.1080/14623730.2008.9721771
Carless, D., Douglas, K., & D., C. (2012). The ethos of physical activity delivery in
mental health: A narrative study of service user experiences. Issues in Mental
Health Nursing, 33(3), 165–171.
https://doi.org/http://dx.doi.org/10.3109/01612840.2011.637659
Carneiro, L. S. F., Fonseca, A. M., Vieira-Coelho, M. A., Mota, M. P., & Vasconcelos-Raposo,
J. (2015). Effects of structured exercise and pharmacotherapy vs. pharmacotherapy
for adults with depressive symptoms: A randomized clinical trial. Journal of
Psychiatric Research, 71(July), 48–55.
https://doi.org/10.1016/j.jpsychires.2015.09.007
Cattan, M., Kime, N., & Bagnall, A. M. (2011). The use of telephone befriending in low
level support for socially isolated older people - an evaluation. Health and Social

Care in the Community, 19(2), 198–206. https://doi.org/10.1111/j.1365-
2524.2010.00967.x
Charlesworth, G., Sinclair, J. B., Brooks, A., Sullivan, T., Ahmad, S., & Poland, F. (2017).
The impact of volunteering on the volunteer: findings from a peer support programme
for family carers of people with dementia. Health and Social Care in the Community,
25(2), 548–558. https://doi.org/10.1111/hsc.12341

