


1
A Qualitative Study Exploring the Effects of Adverse Childhood Experiences on Development
and the Role of Resilience in Shaping Adult Life
Rebecca Anderson
Department of Community Care and Counseling, Liberty University
A Dissertation Presented in Partial Fulfillment
Of the Requirements for the Degree
Doctor of Education
School of Behavioral Sciences
Liberty University
2025

2
Childhood Trauma: The Impact on Development, and How Childhood Trauma Shapes Adult
Life
Rebecca Anderson
A Dissertation Presented in Partial Fulfillment
Of the Requirements for the Degree
Doctor of Education
School of Behavioral Sciences
Liberty University, Lynchburg, VA
Approved by:
Dr. Jason K. Ward, Committee Chair
Lisa Ansell, Ph.D., Committee Member

3
Abstract
This qualitative study investigated the impact of adverse childhood experiences (ACEs) on
development and examines how resilience shapes adult outcomes. Early life experiences
significantly influence an individual's lifelong development, with childhood experiences playing
a particularly crucial role. Adverse childhood experiences, which encompass abuse, neglect, and
household dysfunction, are recognized as a major public health concern due to their association
with health disparities and psychosocial issues in various aspects of life, including substance use,
relationships, education, and employment. Despite these challenges, some individuals
demonstrate remarkable resilience, adapting to new circumstances and maintaining normal
functioning in the face of adversity. Themes from respondents regarding resilience include faith
in God and His transformative work, support from others, having a sense of purpose or calling.
The theme of faith in God highlights the importance of spiritual beliefs and practices in helping
individuals cope with and overcome adverse experiences. Support from others emerged as a
critical factor, emphasizing the role of relationships and social connections in fostering
resilience. Having a sense of purpose or calling, underscores the significance of finding meaning
and direction in life as a means of overcoming adversity. The insights gained from this study
may provide counselors and counselor educators awareness and insights to build on treatment
modalities promoting resilience and validating the work put in by clients who seek to overcome
adverse childhood experiences.
Keywords: adverse childhood experiences, healing, interpersonal trauma, resilience

4
Dedication
To my husband and my children. I am deeply grateful for your steadfast support
during this challenging dissertation journey. Your love, patience, and understanding have
been the foundation that supported me, even in moments when I felt like I might stumble.
My beloved husband, you have been my unwavering support, my trusted confidant, and my
greatest source of encouragement. Your readiness to embrace additional responsibilities,
your reassuring words in times of uncertainty, and your faith in my abilities have been truly
invaluable. Your dedication during countless evenings and weekends has kept our home
running smoothly while I fully involved myself in research and writing. No matter how
difficult the road ahead may have appeared, your love has always been there to help me
strive for greatness.
To my precious children, your innocent smiles and warm hugs have been a balm to
my weary soul. You've grown so much during this process, not just in height but in maturity
and empathy. Your curiosity about my work and your attempts to help, even in small ways,
have been both endearing and motivating. You've inspired me to push harder, to be a role
model worthy of your admiration, and to create a legacy that you can be proud of.
This dissertation is as much yours as it is mine. It stands as a testament to the power
of family, love, and sacrifice. Your support has turned what might have been a lonely and
tough journey into a wonderful adventure of growth and achievement together. As I close
this chapter of our lives, I look forward to the next with excitement and gratitude, knowing
that with you by my side, there is nothing we cannot achieve together. Thank you for being
my inspiration, my comfort, and my home. This achievement is dedicated to you, with all
my love and appreciation.

5
Acknowledgments
Words cannot express my gratitude for my dissertation team Dr. Jason K. Ward and Dr.
Lisa Ansell. Your advice, feedback, and encouragement have been everything to me. This
dissertation would not exist without your dedication to the Lord, the program, Liberty
University, and your students. You were instrumental in this dissertation's concept, development,
and creation. I am forever grateful. Thank you.

6
Table of Contents
Abstract............................................................................................................................................ 3
Dedication........................................................................................................................................ 4
Acknowledgments............................................................................................................................5
Table of Contents.............................................................................................................................6
List of Tables.................................................................................................................................10
List of Abbreviations.....................................................................................................................11
Chapter One: Introduction.............................................................................................................12
Overview........................................................................................................................................12
Background.................................................................................................................................... 13
Situation to Self..............................................................................................................................17
Problem Statement......................................................................................................................... 18
Purpose Statement..........................................................................................................................21
Significance of the Study............................................................................................................... 22
Research Questions........................................................................................................................25
Definitions......................................................................................................................................26
Summary........................................................................................................................................ 27
Chapter Two: Literature Review................................................................................................... 29
Overview........................................................................................................................................29
Related Literature...........................................................................................................................34
Summary........................................................................................................................................ 60
Chapter Three: Methods................................................................................................................ 63

7
Overview........................................................................................................................................63
Design............................................................................................................................................ 63
Research Questions........................................................................................................................67
Setting............................................................................................................................................ 68
Participants.....................................................................................................................................69
Procedures......................................................................................................................................74
The Researcher's Role....................................................................................................................75
Data Collection..............................................................................................................................78
Interviews.......................................................................................................................................79
Data Analysis................................................................................................................................. 81
Trustworthiness..............................................................................................................................83
Credibility.......................................................................................................................... 84
Dependability and Confirmability..................................................................................... 84
Transferability....................................................................................................................85
Ethical Considerations................................................................................................................... 85
Summary........................................................................................................................................ 86
Chapter Four: Findings.................................................................................................................. 89
Overview........................................................................................................................................89
Participants.....................................................................................................................................90
Tachianna...........................................................................................................................91
Vikki..................................................................................................................................94
Mike................................................................................................................................... 97
Patsy...................................................................................................................................98

8
Mikeila............................................................................................................................. 100
Alex..................................................................................................................................103
Dale.................................................................................................................................. 107
Camille.............................................................................................................................108
Results..........................................................................................................................................110
Theme Development........................................................................................................112
Research Question Responses..........................................................................................148
Summary...................................................................................................................................... 152
Chapter Five: Conclusion............................................................................................................ 154
Overview......................................................................................................................................154
Summary of Findings...................................................................................................................154
Discussion.................................................................................................................................... 159
Implications..................................................................................................................................170
Delimitations and Limitations......................................................................................................181
Recommendations for Future Research....................................................................................... 184
Summary...................................................................................................................................... 185
References....................................................................................................................................188
Appendix A: IRB Approval......................................................................................................... 204
Appendix B: Social Media Recruitment...................................................................................... 205
Appendix C: Consent...................................................................................................................206
Appendix D: Interview Questions............................................................................................... 209
Appendix E: Survey Questions (ACEs and Resilience)..............................................................210
Appendix F: Sample Interview Transcript...................................................................................213


10
List of Tables
Table 1: Participants …………………………………………………………………………...123
Table 2: Theme Development ……………………………………………………………...…..125
Table 3: Coding Framework Table …………………………………………………………….128
Table 4: Aspects of Faith ………………………………………………………………………158
Table 5: Themes and Codes ……………………………………………………………………171

11
List of Abbreviations
Adverse Childhood Experiences (ACEs)
Adverse Childhood Experiences Study Questionnaire (ACESQ)
American Psychiatric Association (APA) Diagnostic and Statistical Manual (DSM)
Attention Deficit Hyperactivity Disorder (ADHD)
Borderline Personality Disorder (BPD)
Cambridge Study in Delinquent Development (CSDD)
Centers for Disease Control (CDC)
Child Maltreatment (CM)
Childhood Traumatic Experiences (CTE)
Cognitive Triad Inventory for Children (CTI-C)
Connor-Davidson Resilience Scale (CD-RISC)
Diagnostic and Statitistical Manual (DSM)
Diagnostic and Statistical Manual 5 Text Revision (DSM-5-TR)
Institutional Review Board (IRB)
Intimate Partner Violence (IPV)
Post Traumatic Growth (PTG)
Post Traumatic Stress Disorder (PTSD)
Prefrontal Cortex (PFC)
Sexually Transmitted Disease (STD)

12
Chapter One: Introduction
Overview
According to Hughes et al. (2017), the first study on adverse childhood experiences
(ACEs) found that 6.2% of Kaiser Permanente health plan patients had four or more ACEs and
that 52% of patients had experienced some form of abuse, neglect, or household dysfunction in
the first 18 years of life. A study conducted by Merrick et al. (2018) found that 61.55% of people
reported having at least one ACE, and 24.64% reported having three or more ACEs, based on
data from the Behavioral Risk Factor Surveillance System that was collected from 23 states in
the United States. The findings show that adverse childhood experiences (ACEs) have an impact
on adults. Furthermore, a significant amount of data suggests a correlation between Adverse
Childhood Experiences (ACEs) and the choices individuals make about their lifestyle or
activities that impact their health throughout their lives (Hughes et al., 2017). Despite the
challenges from ACEs, some people are resilient in the face of adversity because they can adjust
and function effectively (Larkin et al., 2014; Salinas-Miranda et al., 2015).
Trauma can have a lasting impact on survivors. Studies have demonstrated that trauma
can have enduring consequences on all areas of a survivor's life for an extended period following
the traumatic event (Greene et al., 2014). It is important to comprehend how individuals develop
from their traumatic experiences, as some survivors may avoid seeking professional mental
health assistance and opt to manage their emotions alone. Seeking care may occur when
individuals feel exhausted or overburdened (Heard-Garris et al., 2018). Survivors may handle
their trauma differently based on demographic factors (Borge et al., 2016). Merrick et al. (2018)
discovered that childhood trauma had a greater impact on adults' mental health and functioning
compared to trauma experienced in adulthood.

13
The purpose of this research was to identify the elements that contributed to the resilience
of individuals who have survived childhood trauma by studying their personal stories. The
significance of this research lies in the insights it offers educators to better support future
students who have experienced childhood trauma by providing them with opportunities to
overcome their own ACEs. This chapter discusses the background of the study, the problem and
purpose statement, situation to self, significance of the study, research questions, and definitions.
Background
The term trauma is derived from the ancient Greek word ηπαῦμα, which often denotes a
physical wound or injury (Carr, 2022). The term "trauma" is used to describe a very stressful
event that is viewed as having a devastating effect on an individual's physical, mental, social, and
spiritual health (Carr, 2022). It frequently results in challenges with mental stability, memory,
self-awareness, and social interaction. Moreover, individuals may encounter symptoms like
flashbacks, avoidance, negative cognitions and emotions, and increased arousal. Traumatic
experiences reflect the innate tendency towards sin in humanity, which is linked to misconduct,
damage, and suffering (Kolk & Bessel, 2014). Nevertheless, it falls under the larger story of
God's authority in determining salvation and can therefore be viewed as a part of theodrauma, a
drama written and directed by God that involves every person, every creature, and everything
God has his hand on in the universe (Carr, 2022).
The repercussions of the brain and body adjusting to stressful and traumatizing
experiences are known as adverse cognitive outcomes (Kolk & Bessel, 2014). Adverse childhood
experiences, as defined by research, include instances of abuse or neglect, living in conditions of
extreme poverty, being in a household where domestic violence occurs, or any other
circumstances that significantly jeopardize the overall welfare of a young child (Oh et al., 2018).

14
These adverse events have the potential to interfere with the development of the brain and
biologicalOsystems, leading to delays in cognitive functioning (Kolk & Bessel, 2014). Timely
identification and intervention in negative childhood events can significantly enhance a child's
overall welfare throughout their entire life, which can have an effect on their cognitive and
spiritual growth (Oh et al., 2018).
The first study question, which asked people to describe how they overcame adverse
circumstances as children, was based on the theory of adverse childhood experiences. Sub-
question 1 asked participants to explain childhood experiences that helped them become
resilient, while sub-question 2 asked participants to describe adult experiences that they believe
were crucial to their development of resilience.
Historical Context
The addition of post-traumatic stress disorder (PTSD) was added to the Diagnostic and
Statistical Manual of Mental Disorders (DSM-III); the term trauma has garnered more attention
despite its lengthy history (A. P. Association, 2013). According to Friedman (2019), the DSM-III
defined a traumatic event as a catastrophe that deviated significantly from the average human
experience. As a result of a revision to the DSM-5-TR, trauma or a traumatic event is now
defined as exposure to actual or threatened death, serious injury, or sexual violence (A. P.
Association, 2013). Originally, the traumas that were recognized post-traumatic stress disorder
(PTSD) were restricted to incidents like rape, combat, natural catastrophes, severe accidents, or
intentional acts of destruction, such as torture and bombs (Kolk & Bessel, 2014). The DSM-V,
published in 2013, broadened the definition of PTSD to include any experience with real or
threatened death, severe injury, or sexual violation, whether one witnessed the event firsthand or
learned about it from a close friend or family member (N. a. P. Association, 2013). A specific

15
criterion for Post-Traumatic Stress Disorder (PTSD) was introduced for children aged six and
younger (N. a. P. Association, 2013).
Researchers in the field of child psychology, Norman Garmezy and Michael Rutter, were
the first to investigate the problem of childhood trauma and its lasting impacts. Although the
impact of specific circumstances, including divorce, poverty, and bereavement, on children was
not the primary focus of Garmezy and Rutter's study, it did examine the trauma aspect of stress
and coping mechanisms (Rousseau, 2023). Childhood trauma received more attention when
research by Dr. Robert Anda and Dr. Vincent Felitti found a high association between adverse
childhood experiences (ACEs) and the mental and physical health of adults (Rousseau, 2023).
The Kaiser Permanente study gathered data from a sample of more than 17,000 individuals to
calculate the number of Adverse Childhood Experiences (ACEs) that each participant had
encountered (Rousseau, 2023). According to Rousseau (2023), the following occurrences are
adverse childhood experiences (ACEs): physical or sexual assault, mental illness, substance
misuse, parental imprisonment, death of a loved one, and childhood maltreatment or neglect.
According to the study, approximately 25% of participants had encountered many ACEs, and
over 90% had encountered one ACE (Rousseau, 2023). Moreover, the study demonstrated that
health problems were more likely to manifest in those with higher ACE scores (Rousseau, 2023).
Following the publication of the report, there was a significant increase in research
focused on the impact of trauma on both children and adults (Ryan et al., 2018). Research has
been done to determine how trauma affects a child's capacity to learn, attendance, and academic
achievement (Bethell et al., 2014). Furthermore, research was conducted to investigate effective
strategies for mitigating the consequences of trauma (Bellis et al., 2018; Moses & Villodas,
2017; Woods-Jaeger et al., 2018). However, currently, there is anOinadequate amount of

16
qualitative research that highlights the experiences of trauma survivors.
Social Context
Following the Anda and Felitti study, additional research has shown that children who
have experienced trauma are more likely to have long-term health problems, abuse substances,
become involved in criminal activities, and become pregnant during their teenage years (Martin
et al., 2017; McInerney & McKlindon, 2014). Anda and Felitti discovered a correlation between
ACEs and several health problems, including chronic obstructive pulmonary disease, hepatitis,
sexually transmitted diseases, intravenous drug use, depression, obesity, attempted suicide, and
sudden death (Borge et al., 2016). Additional long-term impacts of trauma include poor self-
esteem and coping difficulties (Borge et al., 2016).
According to Rousseau (2023), by the age of 16, over two-thirds of young people in the
United States (U.S.) have encountered some form of traumatic event, and 68 percent of those
who admit to having emotional or behavioral disorders have also been adversely affected by
trauma. Research suggests that children residing in impoverished conditions and belonging to
ethnic minority groups are more susceptible to encountering traumaticOchildhood experiences
(van der Kolk, 2014). According to Children Exposed to Violence | Office of Justice Programs,
n.d., a report from the National Task Force on Children Exposed to Violence, around 66% of
children in the United States are impacted by violence, crime, or abuse. Instances of abuse, such
as verbal, physical, or sexual,Oare frequently observed. Childhood trauma is significant in the
present day because a substantial portion of the population has endured adverse
childhoodOexperiences (van der Kolk, 2014).

17
Theoretical Context
The resilience theory developed by Garmezy and Rutter (1983) formed the foundation of
this study. The resilience theory refers to an individual’s capacity to adjust and cope with
difficulties, and resilience theory investigates the elements that enhance a person’s ability to
effectively handle risks or challenges (Masten, 2018). Furthermore, the resilience theory offers a
theoretical framework for understanding how individuals can adapt positively after experiencing
trauma or adversity (Masten, 2018). It emphasizes strengths rather than weaknesses and explains
how human capacity enables individuals to not only survive but also thrive during and after
facing life’s challenges (Masten, 2018). In addition, the resilience theory offers insight into the
reasons why certain individuals are able to effectively manage the impact of their adverse
childhood experiences. The theoretical approach in this study offers a framework for the
development of an understanding of human growth and potential, as well as the relationship
between how an individual’s life works together (Masten, 2018).
Situation to Self
I experienced childhood trauma, including neglect, physical abuse, emotional abuse, and
abandonment. Furthermore, I was born with fetal alcohol syndrome, attention deficit
hyperactivity disorder (ADHD), and learning difficulties. My parents were drug addicts who
spent much of their lives in county jail until they passed away. As a result of spending years in
foster homes and group homes, I left school, began taking drugs, and was convicted of my first
felony at 15. I was in multiple violent relationships throughout the years and ended up as a single
mother of 5 children. At 30 years old, I was introduced to Christ, and my profound love for God
significantly transformed my life. I enlisted in the military to provide a secure future for my
children, but I eventually got out for medical reasons. I utilized my military benefits to register

18
for college. After receiving years of therapy, persistent effort, and acquiring effective learning
strategies, I have successfully overcome adversities. I have a great desire to investigate the lived
experiences of individuals who have survived trauma throughout their childhoods, exploring how
trauma impacted their cognitive developmentOand the lasting impact of childhood trauma on
theirOadult lives.
My decision to choose a phenomenological approach to researching this topic stems from
the following philosophical assumptions: ontological, which addresses the nature of reality and
recognizes that perceptions of reality differ; epistemological, acknowledging that knowledge is
subjective and requiring the researcher to establish a strong relationship with the phenomenon
under study; and methodological, which is informed by the researcher’s experience while
collecting and analyzing data and relies on inductive reasoning (Creswell & Poth, 2018). I
analyzed the findings to identify recurring patterns, supported my claims with quotes from the
participants, and carefully examined the specific details to draw broader conclusions (Creswell &
Poth, 2018). The study was guided by the paradigm of social constructivism, aiming to gain a
comprehensive understanding of the environment in which participants live and work, allowing
me to gain insight into the realities faced by resilient survivors (Creswell & Poth, 2018). To
describe the essence of the phenomenon, I identified commonalities in the data obtained from
these survivors which involved a thorough analysis of interview transcripts, looking for shared
themes and experiences that illuminate the nature of resilience in the face of childhood adversity.
Problem Statement
The problem is that a significant number of people who sustain traumatic experiences
throughout childhood are unable to overcome such experiences and demonstrate resilience as
adults (Blodgett & Lanigan, 2018; Borja et al., 2019). According to Gray et al. (2023), an

19
estimated that one in every three children has been exposed to at least one of the eight adverse
childhood experiences (ACEs) that have been highlighted. The factors that can contribute to
adverse childhood experiences include the divorce or separation of parents, the death of a parent
or guardian, the incarceration of a parent or guardian, family domestic abuse, being a victim or
witness of violence in the neighborhood, the presence of depression in a household member, the
presence of addiction in a household member, and experiencing racism (HRSA, 2019; HRSA,
2020).
According to Gray et al. (2023), a study analyzing data from the Behavioral Risk Factor
Surveillance System revealed significant correlations between adverse childhood experiences
(ACEs) and negative outcomes in adulthood. The research found that individuals with three
ACEs were 1.53 times more likely to not complete high school and 2.4 times more likely to be
unemployed compared to those without ACEs. The impact becomes even more pronounced for
those with four or more ACEs. These individuals face a 1.6 times higher likelihood of living in
poverty, a 2.34 times higher likelihood of not completing high school, and a 2.3 times higher
likelihood of being unemployed (Metzler et al., 2016). These statistics underscore the long-term
consequences of childhood trauma on educational attainment and socioeconomic status in
adulthood. Given the strong association between ACEs and increased risks of academic failure
and adult difficulties, it is crucial for mental health professionals to investigate the factors that
enable some children to overcome trauma. By identifying these resilience-promoting factors,
professionals can develop and implement strategies to support a larger number of individuals
affected by ACEs. This approach could potentially mitigate the long-term negative consequences
of childhood trauma and improve outcomes for those who have experienced ACEs.

20
According to Hardcastle et al. (2018), since the groundbreaking ACE study conducted by
Anda and Felitti, numerous quantitative studies have explored various aspects related to Adverse
Childhood Experiences (ACEs). These studies have examined the prevalence of childhood
trauma and its wide-ranging impacts on individuals’ lives, including physical and mental health
outcomes, academic performance, and behavioral issues (Fry et al., 2018; Hardcastle et al.,
2018). Recent research has also focused on identifying strategies that mental health professionals
and educational institutions can employ to foster resilience and mitigate the long-term effects of
ACEs (Hunt et al., 2017; Sciaraffa et al., 2018). These studies have provided valuable insights
into potential interventions and support systems that can help individuals overcome the
challenges associated with childhood trauma. While the existing literature on ACEs has
significantly contributed to our understanding of their profound effects on various aspects of an
individual’s life, there is a notable gap in qualitative research. Specifically, no studies to date
have gathered in-depth qualitative data from individuals who have successfully overcome trauma
to identify recurring patterns in their lives (Ryan et al., 2018). This gap in literature presents an
opportunity for further exploration and understanding of resilience in the face of childhood
adversity. The comprehensive qualitative data that was obtained in this study offers valuable
insights for professionals working with children experiencing chronic trauma. By examining the
lived experiences of resilient adults who have overcome ACEs, this research may lead to the
development of more effective strategies to assist individuals in becoming resilient adults. Such
findings could have significant implications for intervention programs, therapeutic approaches,
and support systems designed to help those affected by childhood trauma.

21
Purpose Statement
This study was guided by the resilience theory developed by Garmezy and Rutter (1983),
which investigates the process by which individuals cultivate resilience, a characteristic essential
for overcoming traumatic experiences (Masten, 2016). The theoretical framework provided a
lens through which to examine the complex distinction between adversity and positive
adaptation. The research question driving this study is “How do adults who have experienced
childhood trauma describe the essence of their lived experiences?” This question sought to
uncover the significant ways in which individuals perceive, interpret, and make meaning of their
traumatic experiences and subsequent journey towards resilience. The interview questions were
crafted using a combined theoretical approach, offering a comprehensive framework for
understanding human development and potential. This approach recognizes that an individual’s
growth and resilience are influenced by the functioning and interaction of various systems in
their life (Masten, 2016). By exploring these systemic influences, this provided a holistic
understanding of the resilience process. Through in-depth interviews with adults who have
experienced adverse childhood experiences, this research has developed complex pathways of
resilience and recovery. By focusing on the lived experiences of these individuals, this study
contributed valuable insights into the field of trauma research and informative practices for
supporting survivors of childhood adversity.
The resilience theory was chosen because it provides a suitable foundation for conducting
a transcendental phenomenological study on individuals who have successfully overcome
adverse childhood experiences and developed resilience in adulthood. I conducted a qualitative
study to uncover factors that contribute to the phenomenon of resilience. Although there is a
wealth of literature on resilience and on adverse childhood experiences (ACEs), my research

22
adds to the body of knowledge by focusing on ACEs and their impact on resilience. To
investigate lived experiences of resilience, I employed purposive sampling in a basic qualitative
research study. The participants were selected from a variety of online geographic locations in
the Pacific Northwest, which include the states of Washington, Oregon, and California, as a
result of the use of convenience sampling on Facebook. All study participants completed a
screening profile to see whether they met the criteria for participation, using ACE and resilience
self-rating scales. Participants were required to meet the criteria: they must have resided in the
Pacific Northwest for a minimum of ten years, have an ACE count of four or more or one
ongoing ACE, and possess a resilience score that falls within the top two quartiles. Data on age,
gender, race/ethnicity, degree of education, and length of time spent living in the Pacific
Northwest was collected. The qualitative research paradigm, given the complex nature of the
resilience phenomenon, permits the utilization of open-ended questions during semi-structured
interviews to explore personal attributes, protective factors, reactions to stress, utilized resources,
and interpersonal connections that potentially influence an individual’s resilience experience.
Chapter 3 contains further information regarding the characteristics and methodology of the
study.
Significance of the Study
This study aimed to address a significant gap in research by exploring the lived
experiences of individuals in the Pacific Northwest who have both high levels of Adverse
Childhood Experiences (ACEs) and resilience. By gaining a deeper understanding of how
resilience plays a role in overcoming ACEs, this research sought to provide valuable resources
for healthcare providers and improve treatment procedures for individuals with ACEs. The
ultimate goal was to contribute to better overall care and support for ACE survivors, potentially

23
leading to more effective interventions and improved long-term outcomes. Through this
investigation, the study aimed to shed light on the complex interplay between childhood trauma
and resilience, offering insights that could inform both clinical practice and policy decisions in
the field of trauma-informed care.
Recent studies have provided valuable insights into the relationship between adverse
childhood experiences (ACEs) and adult resilience. Daníelsdóttir et al. (2022) conducted a
comprehensive examination of the association between ACEs and various adverse health
outcomes in adulthood. Their research also explored how ACEs contribute to coping abilities and
psychiatric resilience later in life. The primary objective of their study was to determine the
extent of ACEs’ influence on adult outcomes. The findings from Daníelsdóttir et al. (2022)
revealed a significant correlation between cumulative ACE exposure and lower adult resilience.
Importantly, this relationship remained distinct from adult socioeconomic factors and social
support, suggesting that adult resilience may be largely determined during early childhood. The
study also highlighted specific ACEs, such as emotional neglect, bullying, sexual abuse, and
mental illness of a household member, as being consistently linked to reduced adult resilience.
One of the key observations from Daníelsdóttir et al. (2022) was that the associations between
ACEs and adult resilience were only marginally attenuated after controlling for adult
socioeconomic factors and social support. The finding underscores the enduring impact of
childhood experiences on adult outcomes. Complementing these findings, Nishimi et al. (2020,
2021) conducted studies examining the relationships between specific categories and
characteristics of childhood maltreatment and adult resilience capacity and provided additional
nuance to our understanding of ACEs and resilience. Notably, they found that the developmental
timing of maltreatment did not differentially influence resilience capacity. However, Nishimi et

24
al. (2020, 2021) did identify certain types of childhood experiences as particularly detrimental to
adult resilience. Their findings indicated that childhood emotional abuse and the co-occurrence
of multiple types of maltreatment may significantly harm an individual’s capacity for resilience
in adulthood. These studies collectively contribute to a growing body of evidence highlighting
the long-term impacts of adverse childhood experiences on adult resilience and overall well-
being. They emphasize the importance of early intervention and support for children
experiencing adversity to promote better resilience outcomes in adulthood.
Studies have focused on ACEs and resilience; however, most of the studies are
quantitative and focus on either ACEs or resilience separately (Daníelsdóttir et al., 2022; Nishimi
et al., 2020, 2021). Quantitative studies focusedOon ACEs and resilience are essential; however,
the voices of trauma survivors need to be heard (Daníelsdóttir et al., 2022; Nishimi et al., 2020,
2021). Research that is dedicated to the mental, emotional, and spiritual health of ACE victims is
either outdated or lacking, necessitating advocacy and further research (Daníelsdóttir et al., 2022;
Nishimi et al., 2020, 2021). To gain a better understanding of the phenomenon, the lived
experiences of the participants provided insights on how resilience can be achieved (i.e., their
views, difficulties, relationships with loved ones, social support, resources, spirituality, etc.)
throughout adulthood (Zhen-Duan et al., 2023). The gathering insights intended to provide
practical resources for trauma victims who engage in open discussions about their
experiencesOwith their support systems, including friends, family, medical professionals, and
mental health professionals. Additionally, this studyOmayOoffer ways professionalsOcan provide
trauma victims with the proper treatment (Daníelsdóttir et al., 2022; Nishimi et al., 2020, Nishimi
et al., 2021).

25
Several interventions are needed to address adverse childhood experiences (ACEs),
which are deemed a public health problem (Bethell et al., 2017). Programs and resources can be
implemented in various systems, including affordable housing, childcare, healthcare, parenting,
financial assistance, education, and community safety initiatives that address intimate partner
violence,Osubstance abuse, and child abuse (Wade et al., 2014). Research on resilience can also
have a beneficial social change impact on areas such as behavioral and mental healthcare
services, suicide prevention, rehabilitation, trauma-informed treatment, and psychological and
social development (Wade et al., 2014; Zhen-Duan et al., 2023). Given the prevalence of ACEs
and their uncontrollable nature, it is imperative that cultural transformation moves away from a
judgmental mindset that questions, “What is the matter with you?” to a perspective that seeks
comprehension by asking, “What transpired in your experience?” or “What can I do for you?”
(Substance Abuse and Mental Health Services Administration-Health Resources and Services
Administration, 2019).
Research Questions
Research Question 1
Research question one asks, “How do adults who experienced childhood trauma describe
the essence of their lived experiences?” The resilience theory states that specific personality
traits, strong social networks, the ability to overcome adversity, and positive relationships are the
main components of resilience (Masten, 2018; van Breda, 2018). The researcher looked for
commonalities of personality, social networks, and intrapersonal relationships in life that helped
participants overcome adversity and develop resilience (Naeem et al., 2023).
Sub-question 1

26
Sub-question one asks, “What are the perceived long-term effects of childhood trauma on
the lives of adults, as revealed through their firsthand accounts and reflections?” Research has
demonstrated that traumatic experiences in childhood can lead to negativity and a lack of faith in
one’s own abilities to overcome adversity (Masten, 2018). The researcher looked for common
themes during adolescence and adulthood that help individuals overcome these limitations,
cultivate resilience, and become productive members of society (Naeem et al., 2023).
Sub-question 2
Sub-question two asks, “How do adults who experienced childhood trauma describe how
their experiences have shaped their understanding of themselves and their world?” The life
experiences of study participants, both positive and negative, was considered as they recount the
events that have molded their identities (Masten, 2018). The participants were requested that
they reflect on the experiences they have had throughout their adult lives up to this point and
describe which experiences made a significant contribution to their achievement (Naeem et al.,
2023). For the purpose of the study, the researcher looked for common themes, which was
supplied with the data (Naeem et al., 2023).
Definitions
1. Adverse Childhood Experiences (ACEs) – The term “adverse childhood experiences”
refers to events or experiences that occur during childhood and have lasting negative
impacts (Souers & Hall, 2016).
2. Childhood Traumatic Experiences (CTE) – There are various types of experiences that
might be classified as adverse childhood experiences. These scenarios encompass, but are
not restricted to, the following: “emotional abuse, physical abuse, sexual abuse,
emotional neglect, physical neglect, domestic violence toward the youth’s mother,

27
household substance abuse, household mental illness, parental separation/divorce, and
household member with a history of jail/imprisonment” (Baglivio et al., 2017).
3. Posttraumatic Growth (PTG) – is the process by which an individual who has survived a
traumatic event undergoes a profound personal growth.O“Difficulty bouncing back
experiences a traumatic event that challenges his or her core beliefs, endures
psychological struggle… and then ultimately finds a sense of personal growth” (Collier,
2016).
4. Resilience – is the method by which people respond to stressors such as trauma,
adversity, or other situations (American Psychological Association, 2013). According to
Collier (2016), resilience is a trait of character that allows people to overcome adversity
without having to “rocked to the core by an event and doesn’t have to seek a new belief
system” (p. 48).
5. Survivor – is a term that can be used to describe resilience and is empowering for people
who have endured trauma (Newsom & Myers-Bowman, 2017).
Summary
In summary, this hermeneutic phenomenological study aimed to analyze the firsthand
experiences of individuals who overcame Adverse Childhood Experiences (ACEs) in adulthood.
ACEs are widely recognized as a significant public health concern, often resulting in unfavorable
medical conditions (Salinas-Miranda et al., 2015; Wade et al., 2014). However, research suggests
that some people can remain resilient and function effectively despite facing adversity (Borge et
al., 2016), and resilience may be more prevalent than previously thought (Southwick et al.,
2014). To gain an in-depth understanding of resilience in the context of ACEs, this study focused
on the personal experiences of individuals in the Pacific Northwest who have experienced a high

28
number of ACEs but have also demonstrated resilience. By examining these lived experiences,
the research aimed to provide valuable insights into the development and maintenance of
resilience in the face of childhood adversity. The results of this study can be utilized to guide the
development of resilience intervention strategies, practices, and programs that seek to facilitate
positive social transformation. While there has been an increasing amount of research conducted
on ACEs, no qualitative studies specifically addressing this topic were found, highlighting the
unique contribution of this research.
Subsequent chapters will provide a more comprehensive examination of the areas
discussed in chapter one, including the significance of the study, the purpose of the study,
research questions, literature review, and assumptions and limitations. Later chapters will delve
into individual interview responses, thematic analysis, and discussion of the findings. By
exploring the lived experiences of resilient adults who have overcome ACEs, this study aims to
contribute to the growing body of knowledge on resilience and inform strategies for supporting
individuals who have experienced childhood trauma.

29
Chapter Two: Literature Review
Overview
This chapter seeks to present literature as foundational components to the nature of the
proposed study, to include background information related to the detrimental effects and
hindrances to optimal growth and development caused by the existence of toxic stress, trauma,
and childhood adversities (Salinas-Miranda et al., 2015; Wade et al., 2014). Adverse Childhood
Experiences include various forms of maltreatment such as abuse or neglect, severe poverty,
residing in a household with domestic violence, or other circumstances that significantly
jeopardize a child’s welfare (Bethell et al., 2017; Wade et al., 2014). This chapter will examine
the long-lasting impact that ACEs can have on individuals, disrupting various aspects of
development including cognition, mental health, physical well-being, and neurobiological
functioning (Sacks et al., 2014).While certain individuals may experience physical, behavioral,
mental, financial, legal, and social complications as a result of ACEs,Oothers are resilient and
continue to function effectively in the face of adversity (Harper-Browne, 2014).
Several studies have linked adverse childhood experiences (ACEs) to adult morbidity and
mortality, as well as to health disparities across a person’s lifespan (Salinas-Miranda et al., 2015;
Wade et al., 2014). Findings from the studies have led to the conclusion that ACEs constitute a
public health crisis (Bethell et al., 2017). Some examples of the many forms of hardship that
people face include abuse and neglect of children and dysfunction in the home, including
substance misuse and violence against women (Sacks et al., 2014). Although ACEs can have
long-lasting consequences, such as physical, behavioral, mental, financial, legal, and social
difficulties for certain individuals, there are also resilient individuals who are able to maintain
their well-being despite facing adversity (Harper-Browne, 2014).

30
A systematic review of the literature was conducted to explore the problem of long-term
negative effects of adverse childhood experiences, in addition to factors that promote an ability
to become resilient. According to Wade et al. (2014), the resilience theory by Garmezy and
Rutter (1983) discusses the first section guiding the framework for this study. The following
section will provide a review of the most recent literature on the long-term effects of adverse
childhood experiences and the role of resilience in reducing the impact of childhood trauma.
Additionally, this chapter examines the literature about Adverse Childhood Experiences and
resilience, describes what is known about the relationship between the two, and identifies the
gaps in the knowledge that warrant further research into the phenomenon of the experience of
resilience following adverse childhood experiences.
Theoretical Framework
Resilience Theory
The resilience theory serves as the theoretical framework for understanding why some
individuals overcome adversity and become resilient adults (Masten, 2016). According to
Masten (2016), the field of resilience science emerged in the 1970s. The Kauai Longitudinal
Study, an interdisciplinary inquiry and signature resilience study of infants born in 1955 on
Kauai, Hawaii (Werner, 1989). The study examined the long-term effects of perinatal and
prenatal problems, child development, and adaptations from birth to adulthood (Masten, 2016).
Studies have indicated that children who grow up in poverty are more susceptible to
experiencing negative health and developmental delaysO(Masten, 2016). Numerous
environmental and internal resilience factorsOwere found in this study’s additional findings.
According to Masten (2016), internal characteristics included family members’ affection,
emotional support, intelligence, sociability, activity level, and theOcapacity for communication.

31
Social networksOat home, in the workplace, and at church were considered external factors
(Masten, 2016). In general, theory explains how people can make positive changes after going
through trauma or hardship (Masten, 2016). It focuses on strengths instead of weaknesses
(Masten, 2016) and is used to explain how people can survive and thrive during and after going
through life’s challenges (Masten, 2016).
According to Masten (2016), the expansion of resilience theory can be attributed to the
following factors: an increase in the number of scientific studies, an evolving definition of
resilience, and its association with developmental science and systems theory. The history of
resilience science contributes to our understanding of why some siblings or children perform
better than other childrenOwhen they are exposed to the same traumaO(Masten, 2016). Resilience,
as described by Masten (2016), refers to the ability to effectively adapt to disruptions that pose a
threat to the functioning, survival, or growth of a system. Interactions among different systems
can establish avenues of influence that contribute to an individual’s ability to adapt and maintain
good health during or after experiencing adversity (Masten, 2016). Therefore, an individual’s
ability to adapt effectively relies on multiple systems, rather than justOcharacteristics or
resources.
Resilience can be defined as the capacity to endure and recover from challenging
situations, maintaining a stable state of well-being even after experiencing highly adverse events
(Southwick et al., 2014). It also involves utilizing available resources to sustain one’s overall
health and happiness (Heard-Garris et al., 2018). Therefore, resilience is more than just being
healthy or not having any problems. While a clear definition of resilience has not been
universally agreed upon, certain characteristics have been identified as protective and conducive
to resilient outcomes (Heard-Garris et al., 2018). These consist of problem-solving skills, self-

32
worth, confidence, self-determination, self-control, and supportive relationships (Heard-Garris et
al., 2018). According to Southwick et al. (2014), it is crucial to determine whether the term
resilience is being used to describe a characteristic, a series of actions, or an outcome. They
propose that resilience exists on a spectrum across various aspects of life, including work, health,
and interpersonal connections (Southwick et al., 2014).
According to Heard-Garris et al. (2018), a factor is deemed protective if it lowers the
impact of a risk factor. Both internal and external aspects of a person’s life can be considered
protective factors (Heard-Garris et al., 2018). Examples of protective factors include good
parenting, relationships with other competent adults, intellectual abilities, self-efficacy, self-
worth, optimism, religious or faith affiliations, socioeconomic advantages, a good education, and
other community assets (Masten, 2016). Moreover, risk factors are those that can interfere with a
person’s development and functioning, which can lead to negative outcomes and distress
(Southwick et al., 2014). Common risk factors that are often the subject of research include
poverty, familial instability, low educational attainment, single parenthood, and medicalOissues
(Southwick et al., 2014). Protective factors, like risk factors, vary in nature but still have a
combined impact.
Protective factors have the potential to enhance an individual’s resilience and lower their
likelihood of illness or mortalityO(Braveman & Gottlieb, 2014). In addition to the previously
listed protective factors, other factors include interpersonal support, self-worth, genetic and
biological factors, financial and social resources, personality traits, caregiver bond, positive
attachment style, capacities for emotional regulation, goal-driven, and intrinsic motivation
(Braveman & Gottlieb, 2014). Self-efficacy, a person’s spirituality, coping style, and personality,
like being an extrovert and having a good attitude, were all found to be predictors of growth

33
(Southwick et al., 2014). Following a traumatic experience, it is possible for an individual to
experience personal growth in their relationships, self-perception, and philosophy of life
(Braveman & Gottlieb, 2014).
Masten (2016) collected data from the Kauai Longitudinal Study and identified several
characteristics shared by resilient children. These include having a positive role model
relationship or a strong attachment to a caregiver; having an easygoing, affectionate, adaptable,
and good-natured temperament; having a large social circle in elementary school; and having
above-average cognitive abilities in areas like language and reasoning. Researchers agree that
resilience is not reducible to individual traits or characteristics but rather a phenomenon that can
be attained through various pathways (Masten, 2016). According to Masten (2016), the
comprehensive data on resilience demonstrate that individuals are capable of overcoming
adverse environmental circumstances in order to lead healthy lives, despite the risks that they
face.
According to the researchers, an ecological approach should be used in any future
resilience-related research (Masten, 2016). Masten (2016) concluded that resilience may be
applicable across system levels, since problems can happen at different levels in one’s
ecosystem. The interaction between systems can establish pathways of influence that enable an
individual to experience healthy adaptation during or after adversity (Masten, 2016). The impact
of intersystem interactions on human development can be better understood through a framework
that combines ecological systems theory with resilience theory (Masten, 2016). To researchOthe
connection between adverse childhood experiences (ACEs) and the level of resilience that
parents perceive in their children, Heard-Garris et al. (2018) utilized Bronfenbrenner’s ecological
system theory in addition to theOresilience theory. This was accomplished by analyzing the

34
factors that are associated with child resilience at the child, family, and community levels.
Heard-Garris et al. (2018) discovered that there is a direct correlation between adverse childhood
experiences (ACEs) and resilience. This means that the number of ACEs a person has will affect
their ability to endure, adjust, or recover from difficult situations. The resilience theory is
relevant to my study, which will look at the lives of people who have ACE’s high resilience
scores (Southwick et al., 2014). The livedOexperiences of people with high resilience scores and
ACE exposure will beOexamined in this studyOin order to add to the body of literature already in
existence using the resilience theory.
Related Literature
Adverse Childhood Experiences (ACEs)
Vincent Felitti and his associates conducted groundbreaking research that is frequently
referred to as the ACEs study (Souers & Hall, 2016). Their goal was to study the correlation
between health risk behavior and disease and the incidence of emotional, physical, or sexual
abuse and household dysfunction in childhood and the mental and physical well-being
inOadulthood (Souers & Hall, 2016). The study discovered a connection between the level of
childhood abuse or dysfunction in the home and various adult risk factors for several of the top
causes of mortality (Kelly-Irving & Delpierre, 2019). Adverse childhood experiences include
many forms of abuse, neglect, and other traumatic events during childhood that have long-term
effects on one’s mental and physical health (Sciaraffa et al., 2018). According to Souers and Hall
(2016), the phrase is frequently used interchangeably with maltreatment or childhood trauma.
The Centers for Disease Control (CDC) and Kaiser Permanente collaborated to create and
evaluate the ACE scale, which measures adverse events in participants' childhoods, and this led
to the phenomenon's initial public recognition (Felitti et al., 1998b).

35
The Adverse Childhood Experiences (ACE) Study analyzed information from surveys
filled out by more than 9,000 adults on their risky behaviors, health, and diseases because of
trauma they experienced as children (Sacks et al., 2014). According to previous research, this
study included the following adverse childhood experiences: physical, psychological, or sexual
abuse; intimate partnerOviolence; living with family members who abused substances, had mental
illness, were suicidal, or had ever been in prison; the death of a parent or loved one; or marital
separation or divorce (Bernard et al., 2020). The CDC-Kaiser Permanente Study’s participants
were mostly white, college-educated, and had access to great healthcareO(Dube, 2020; Ports et
al., 2020). The results indicated ACE occurs across individuals across all demographic groups,
rather than being limited to those who are raised in economically disadvantaged households.
According to the findings of Sacks et al. (2014), nearly two-thirds of individuals who replied had
encountered one ACE, and a quarter had encountered two or more. The findings also revealed
that adults with four or more ACEs had a twelve-fold increased risk of alcoholism, drug abuse,
depression, and attempted suicide; they also had a two- to four-fold increased risk of smoking,
self-rating as unhealthy, having fifty or more sexual partners, having STDs, and being severely
obese (Sacks et al., 2014). The researchers discovered a direct correlation between the amount of
adverse childhood experiences (ACEs) a person had and the likelihood of developing health
problems in adulthood, including heart disease, lung illness, cancer, bone fractures, and liver
disease (Sacks et al., 2014). The participants in the study also self-reported a low ranking of their
overall health (Sacks et al., 2014). The major findingOof this study was that Adverse Childhood
Experiences (ACEs) play a crucial role in determining the overall health and socioeconomic
welfare of the nation (Waite & Ryan, 2019).

36
According to Crouch et al. (2019), a total of nine adverse childhood experiences (ACEs)
were considered in this study. These were parental death or separation, exposure to domestic
violence, mental illness, imprisonment, or drug misuse, exposure to neighborhood violence,
racial mistreatment, and poverty. The list of adverse childhood experiences (ACEs) was
expanded in other research to include emotional and physical neglect (Sacks et al., 2014). The
list of extended adverse childhood experiences (ACEs) now includes being a foster child and
having experienced bullying (Waite & Ryan, 2019). Despite its strong associations with other
adverse childhood experiences (ACEs), homelessness has not been officially recognized as one
yet (Radcliff et al., 2019). According to Sacks et al. (2014), the initial ACE study opened the
door to a great deal of empirical curiosity regarding the complicated,Odetrimental, and long-
lasting consequences of adverse childhood experiences. According to Kelly-Irving and Delpierre
(2019), between 1985 and 2018, the number of articles with Adverse Childhood Experiences in
the title rose from one in 1985 to two hundred. Among other findings, a recent study conducted
by Struck et al. (2021b) that analyzed the relative health of research within the ACE field, which
involved examining publications and features of peer-reviewed research on the topic, revealed
that there were 789 articles between 1998 and 2018.
Expanded ACE Studies
According to Merrick et al. (2019), data from the Behavioral Risk Factor Surveillance
System, which was conducted from 2015 to 2017, showed that 15.6% of adults had experienced
four or more ACEs, while 60.9% of adults had experienced at least one ACE. If someone has
experienced one Adverse Childhood Experience (ACE), there is an 87% chance that they will
also report experiencing at least one more ACE (Ports et al., 2020; Waite & Ryan, 2019).
Multiple research projects have indicated that adolescents living in poverty and belonging to

37
ethnic minorities are more prone to having adverse childhood experiences (Ijadi-Maghsoodi et
al., 2017; Larson et al., 2017; Ports et al., 2020; Walsh et al., 2019). Approximately 66% of
children in the United States have experienced some sort of violence, crime, or abuse, including
sexual assault, physical attacks, domestic violence, andOviolence in the community (Martin et al.,
2017). Behavioral Risk Factor Surveillance System research shows that sexual assault, physical
violence, and verbal assault are all common forms of abuse among young people (Martin et al.,
2017). According to Baglivio et al. (2020), the number of children in the United States who were
the subject of Child Protective Services investigations in 2018 was close to 4 million, indicating
the frequency of child abuse in this nation. Furthermore, Crouch et al. (2019), shared that the
2019 NSCH data revealed that parental divorce or separation affected 21.9% of the children,
whereas economic difficulty was the most common adversity faced by 22.5% of participants.
Moreover, a recent study revealed that women have a greater probability of experiencing four or
more Adverse Childhood Experiences (ACEs), while those aged 18 to 34 have a higher
possibility of having any ACEs (Merrick et al., 2019; Waite & Ryan, 2019). The high incidence
of Adverse Childhood Experiences (ACEs), particularly among younger generations, reinforces
the need to understand how certain individuals are able to overcome the effects of childhood
trauma (Merrick et al., 2019). This knowledge will enable us to support others in overcoming
and preventing the negative consequences associated with childhood trauma.
ACEs and Cognitive Delays
Children’s lifelong well-being can be significantly enhanced by early identification and
treatment of childhood stressors (McKelvey et al., 2018). Adverse cognitive outcomes refer to
the negative effects that the brain and body suffer as a result of adapting to stressful and
traumatic experiences (McKelvey et al., 2018). According to Arnekrans et al. (2018), childhood

38
adversities, such as abuse, neglect, extreme poverty, exposure to domestic violence, or any other
situation that seriously endangers a young child’s well-being, can interfere with the development
of the brain and biological systems, leading to delays in cognitive functioning. Neurobiological
systems can be adversely affected by childhood trauma (McKelvey et al., 2018). The purpose of
the systematic review that was carried out was to gain a better knowledge of the health outcomes
that are connected with childhood adversity in children (McKelvey et al., 2018). The researchers
conducted a comprehensive analysis of pertinent literature that investigated different negative
childhood experiences and their impact on biological health outcomes before the age of twenty
(McKelvey et al., 2018). The study omitted mental, behavioral, and physical health outcomes in
order to exclusively concentrate on cognitive and biological functioning (McKelvey et al., 2018).
The analysis found a total of 15,940 records and 35 studies and indicated that being exposed to
early adversities is linked to cognitive development delays, asthma, infection, sleep disruption,
andOsomatic complaints (McKelvey et al., 2018). To be more precise, challenges such as
dysfunction within the home and abuse have been found to impact weight (McKelvey et al.,
2018). Additionally, maternal mental health problems have been linked to elevated cortisol
levels, whereas mistreatment has been associated with reduced cortisol levels (McKelvey et al.,
2018). McKelvey et al. (2018) study emphasizes the need to consider a child’s history of
adversities in the diagnosis of developmental delays.
ACEs and Brain Development
Research by Cross et al. (2017) investigates the potential long-term effects of early-life
trauma on brain development, specifically how it might influence changes in the amygdala,
prefrontal cortex, and hippocampus. The amygdala is a complex, almond-shaped structure in the
temporal lobe of the brain that’s involved in many aspects of emotion, learning, memory, and

39
fear (AbuHasan et al., 2023). The prefrontal cortex (PFC) has extensive connections with other
brain regions, allowing it to effectively govern our thoughts, behaviors, and emotions (Arnsten,
2009). The complex structure of the hippocampal brain is deeply ingrained in the temporal lobe.
It plays a significant part In memory and learning (McKelvey et al., 2018). The long-term effects
of early life trauma and brain development are in line with the findings of Oh et al. (2018), who
investigated the effects of childhood abuse on cognitive development. By analyzing the
neurobiological development of children who have encountered various forms of toxic stress and
trauma, Cross et al. (2017) offer a more thorough understanding of how childhood adversities are
known to affect development. Cross et al.’s (2017) study not only investigates the effects of
trauma on cognitive development but also explores the detrimental effects it can have on the
physical and mental health of children due to extended and repetitive exposure. Exposure to
violence, neglect, or abuse by caregivers and family members throughout childhood can lead to
changes in neurobiological development, as neurobiological systems are susceptible to the
detrimental effects of developmental trauma (Cross et al., 2017).
Child exposure to interpersonal trauma, as opposed to non-interpersonal trauma, was the
primary emphasis of interpersonal trauma that is more likely to occur throughout development
and take on numerous forms (Cross et al., 2017). The study conducted by Cross et al. (2017)
examined the long-term effects of trauma exposure on the brain development of children. The
research found that such exposure can result in alterations to the structure and function of stress-
sensitive regions, including the hippocampus, prefrontal cortex, and amygdala (Cross et al.,
2017). These alterations can result in a heightened susceptibility to dissociation and disorders
associated with trauma, including symptoms of post-traumatic stress disorder and depression
(Cross et al., 2017). These alterations can impact neurobiological systems across an individual’s

40
entire life and can impede their ability to cope with future stressors (Cross et al., 2017).
Rosenthal et al. (2020) discussed the potential risks of childhood trauma and the trauma-
psychosis cycle for delayed development and cognitive decline in later life. The study suggests
that there is an interacting association between inferior developmental and cognitive trajectory,
childhood trauma exposure, and an elevated risk of psychosis (Rosenthal et al., 2020). Such
relationships are referred to as the trauma-psychosis cycle (Rosenthal et al., 2020). Psychosis can
also be linked to cognitive impairments in intellectual capacity, verbal and nonverbal
memory,Oexecutive function, attention,Oand motor skills (Rosenthal et al., 2020). Further, the
study investigated the effects of atypical development andOchildhood traumaOon the occurrence of
early psychosis and indicated that childhood trauma was linked to an earlier onset of full-
threshold psychosis, a higher number of hospitalizations, an escalation of negative symptoms,
and an elevated likelihood of engaging in self-inflicted harm (Rosenthal et al., 2020). Individuals
with atypical development exhibit an earlier occurrence of psychosis and negative symptoms, as
well as a higher probability of engaging in non-suicidal self-injury (Rosenthal et al., 2020).
However, the combination of childhood trauma and atypical development is more strongly
linked to an earlier onset of symptoms and poorer psychosocial functioning (Rosenthal et al.,
2020). Rosenthal et al. (2020) identified specific risk indicators that might be utilized to
determine targets for treatment and intervention.
Cognitive Delays and Poverty
Literature has discussed the influence of early adversity on development, while other
research conducted indicated more comprehensive investigations into childhood trauma and
focused on various types of trauma and their effects on development (Arnekrans et al., 2018).
The effects of living in impoverished and low-income environments were investigated in a study

41
conducted by De los Reyes-Aragon et al. (2016), where genetic factors were found that largely
influence human development in the early years of life as well as poverty. The study intended to
investigate the developmental levels of children residing in low-income, rural settings and
involved 629 children, ranging in age from zero to five years old. The assessment tool used to
evaluate their development was the Battelle Developmental Inventory. The findings indicated
that 17% of the participants exhibited a delay in their development, particularly in cognitive
development (35.5%) and communication (21.5%) (De los Reyes-Aragon et al., 2016). The
study found that poor social situations tend to promote the growth of the social domain while
restricting the development of the cognitive domain (De los Reyes-Aragon et al., 2016).
De Souza Morais et al. (2021) conducted a study to examine the impact of socioeconomic
conditions and environmental quality on the motor and cognitive development of 147
socioeconomically disadvantaged children from impoverished backgrounds. The children ranged
in ages from 24 to 36 months and who were enrolled in a public childcare facility. The study
employed the Bayley-III Scales, the Home Observation for Measurement of the Environment
Inventory, the Infant/Toddler Environment Rating Scale-Revised Edition, a socioeconomic
indicator, and a custom-designed questionnaire on neighborhood quality.
The findings showed that a person's environmental context affected how they developed
cognitively and that, in order to support the cognitive development of children from low-income
families, public policy coordination between the health, education, and social assistance sectors
is essential (De Souza Morais et al., 2021). De Souza Morais et al. (2021) assert that the
surroundings in which children reside and engage in recreational activities play a vital role in
their physical, psychological, and intellectual growth. Adverse conditions and the setting in
which one grows up can have a detrimental impact on all aspects of development (De Souza

42
Morais et al., 2021). During early childhood, the brain undergoes significant neurophysiological
reorganization, creating a period of immense developmental potential (De Souza Morais et al.,
2021). Children from socioeconomically deprived backgrounds may encounter dangerous risk
factors that impair their success in school.
The impact of poverty on the lives of many children requires further advancements and
innovative approaches, informed by a diverse range of scientific facts (Pollak & Wolfe, 2020).
Approximately 20% of children in the United States reside in households that fall below the
official federal poverty limits, while over 40% of children live in households that are either poor
or close to being poor (Pollak & Wolfe, 2020). Pollak and Wolfe (2020) argue that childhood
poverty is a global issue with significant implications for humanitarian efforts, public health, and
practical considerations. The research indicates that children from low-income homes exhibit
inferior performance across various indicators of academic accomplishment, including school
readiness, grades, and standardized test scores (Pollak & Wolfe, 2020). The long-term
consequences persist throughout adulthood and manifest in reduced income, deteriorating health,
and diminished psychological welfare.
ACEs and Toxic Stress
Toxic stress is the primary cause of harmful health results resulting from ACEs. Toxic
stress refers to the physiological and psychological response that occurs when an individual
experiences prolonged and overwhelming stress that exceeds their ability to cope (van der Kolk.,
2014). Furthermore, persistent exposure to excessively high levels of stress hormones that are
harmful to the body, particularly during adolescent and child development, is known as toxic
stress (Waite & Ryan, 2019). According to van der Kolk (2014), this reaction is also referred to
as the fight/flight/freeze response. Due to continuous exposure to trauma, this particular stress

43
response persists for an extended duration, resulting in a more significant impact. Researchers
have shown that exposure to toxic stress can disrupt normal brain function and that this can have
long-term effects on a person’s physical and mental health, including problems with learning and
behavior (Dube, 2020; Ports et al., 2020; Waite & Ryan, 2019).
In the first five years of life and again between the ages of fifteen and twenty-five, brain
development is more vulnerable to the effects of trauma (Waite & Ryan, 2019). Individuals
diagnosed with posttraumatic stress disorder (PTSD) experience persistent secretion of elevated
levels of stress hormones even after the cessation of the threat or danger, and these hormone
levels do not revert to normal once the threat has passed (van der Kolk., 2014). Memory,
attention, mood, and sleep problems result from a prolonged rise of stress hormones (van der
Kolk, 2014; Waite & Ryan, 2019). Furthermore, prolonged exposure to these stress hormones
has a detrimental effect on the individual’s capacity to self-regulate, cope, and respond to stimuli
(Waite & Ryan, 2019). Those who have suffered from long-term trauma may find it difficult to
emotionally invest in the world around them since this stress affects the part of the brain
responsible for feeling alive (van der Kolk., 2014). Research has demonstrated that issues in any
of these areas can impact a person’s social interactions, academic achievement, mental health,
and overall growth and functioning (Waite & Ryan, 2019).
ACEs and Physical Health
Many studies have analyzed the effects of adverse childhood experiences (ACEs) on
physical health since the initial ACE study (Hughes et al., 2017). Multiple studies have shown
that traumatic events in infancy are among the leading causes of illness and death (Merrick et al.,
2019; Metzler et al., 2016). Toxic stress is a key component of adverse childhood experiences
(ACEs), and this effect becomes even more pronounced with repeated or extended ACEs (Harris,

44
2018; Hughes et al., 2017). Adverse childhood experiences (ACEs) can disrupt the body’s ability
to grow and maintain optimal health by changing gene expression, immune system function,
brain connectivity, and organ function (Merrick et al., 2019). Childhood trauma survivors are
more likely to experience diabetes, obesity, cancer, heart disease, lung disease, and other chronic
illnesses (Hughes et al., 2017; Merrick et al., 2017). There is a strong correlation between a
disrupted stress response and higher levels of inflammation and autoimmune disorders (Harris,
2018). According to Harris (2018), those who have encountered several adverse childhood
experiences (ACEs) are more than twice as likely to have been hospitalized due to an
autoimmune illness as those who have not. Chronic pain, migraines, gastrointestinal problems,
irritable bowel syndrome, and chronic fatigue are among the other health concerns that are
prevalent in those who have endured long-term trauma (van der Kolk, 2014). Children who have
experienced trauma are fifty times more likely than their peers to have asthma (van der Kolk,
2014). Additionally, individuals who have experienced repeated adverse childhood experiences
(ACEs) are at a 57% to 80% higher risk of early death (Vig et al., 2020). Moreover, a study
conducted by Crouch et al. (2019) revealed that those who were exposed to family dysfunction,
along with physical and psychological abuse during their upbringing, exhibited the highest
likelihood of reporting bad health.
Additionally, research has shown that people with a history of traumatic events in
childhood are more likely to engage in risky behaviors such as eating disorders, smoking,
substance misuse, and sexual experimentation (Hughes et al., 2017; Merrick et al., 2019; Vig et
al., 2020). Adolescents who have experienced childhood trauma are at a higher risk of
developing obesity, engaging in teenage pregnancy, or becoming fathers (Harris, 2018; Wekerle
et al., 2020). Furthermore, young adults who have had ACEs are more likely to experience

45
problems related to their reproductive system, including urogenital health disorders and STDs
(Wekerle et al., 2020). According to Wekerle et al. (2020), adolescents who experienced neglect
were more prone to engaging in sexual activity before the age of 13. The probability of early
sexual activity was much higher for individuals who were victims of childhood sexual abuse
(Wekerle et al., 2020).
According to Radcliff et al. (2019b), there is a strong correlation between individuals
who had endured emotional, sexual, and physical abuse and their likelihood of reporting health
issues. Research has demonstrated that adverse childhood experiences (ACEs) increase the risk
of complications during pregnancy, including low birth weight, early birth, and miscarriage
(Harris, 2018). It is crucial to understand that most health effects caused by adversities are a
result of the overall cumulative load, rather than the impact of any single incident (Hamby et al.,
2020). Complex trauma often results in a multitude of psychological and physical issues for
individuals, which can have long-lasting detrimental effects on their quality of life (Harris,
2018).
ACEs and Mental Health
It is crucial to understand that most health effects caused by adversities are a result of the
overall cumulative load, rather than the impact of any single incident (Hamby et al., 2020).
Complex trauma often results in a multitude of psychological and physical issues for individuals,
which can have long-lasting detrimental effects on their quality of life (Hamby et al., 2020). In
the same way that adverse childhood experiences (ACEs) are associated with poor physical
health, they are also associated with mental health problems and problematic behavior incidents
(Hamby et al., 2020). Exposure to toxic stress and early adversity is associated with a reduction
in physiological responses, including the stress response, which can lead to a decline in mental

46
health and wellbeing (Merrick et al., 2017). Larson et al. (2017b) found that childhood trauma
increases the likelihood of mental health disorders and decreases academic performance.
Specifically, they found that youth from low-income and/or racial/ethnic minority backgrounds
who have experienced trauma or victimization are more likely to develop anxiety, depression,
disruptive behavior, psychological disorders such as post-traumatic stress disorder (PTSD),
thoughts of suicide, attention deficit hyperactivity disorder (ADHD), and lower grade point
averages compared to their non-abused peers (Larson et al., 2017).
In a study conducted by Harris (2018), it was discovered that those who experienced four
or more Adverse Childhood Experiences (ACEs) were 32.6 times more prone to being diagnosed
with an intellectual or psychological problem. Due to emotional dysregulation, adults had more
anxiety when adverse childhood experiences (ACEs) were present (Poole et al., 2018). The ACE
most strongly linked to major depressive disorder (MDD) was emotional abuse, according to
another study conducted by these same researchers that indicated 41% of people with depression
had Ied four or more ACEs (Poole et al., 2018). The study conducted by Crouch et al. (2019)
revealed that those who experienced emotional, physical, and sexual abuse during their
childhood were more prone to reporting symptoms of stress, anxiety, and other mental health
problems. According to Sheffler et al. (2020), ACEs can worsen psychotic symptoms and
increase the likelihood of suicidal thoughts and behaviors.
Moreover, individuals who have experienced childhood maltreatment are more prone to
developing a negative cognitive style characterized by self-criticism, which frequently results in
depressive disorders (Sheffler et al., 2020). Mood disorders, post-traumatic stress disorder
(PTSD), substance misuse, personality problems, and a negative way of thinking are frequently
associated with difficulties in controlling one’s emotions (Sheffler et al., 2020). Sheffler et al.

47
(2020) found that a significant proportion of individuals, specifically 82%, who had received a
diagnosis of personality disorder also disclosed experiencing child maltreatment or neglect.
Psychological disorders are often accompanied by substance misuse, such as tobacco, alcohol, or
drugs, which individuals turn to as a means of self-medication for depression and emotional
regulation (Merrick et al., 2017).
According to multiple research studies, there is a consistently high correlation between
childhood adversities and depressive disorders in adults (Merrick et al., 2018; Sheffler et al.,
2020). Merrick et al. (2017) found that the expanded ACE score and the probability of drug use,
moderate to severe drinking, suicidal thoughts, and depression in adulthood have a graded dose-
response connection. In a study conducted by Loudermilk et al. (2018), it was discovered that
adults who experienced childhood abuse had a 30% higher likelihood of engaging in binge
drinking and a 21% higher likelihood of consuming alcohol compared to those who did not
experience such abuse. A new study found that adverse childhood experiences (ACEs) are
already strongly linked to drug abuse and homelessness (Moss et al., 2020).
Post-traumatic stress disorder (PTSD) is more common in individuals who experienced
adverse childhood experiences (ACEs), and it is more common in those who experienced sexual
abuse as children (Sheffler et al., 2020). These individuals also have a higher risk of depression
and addiction (Sheffler et al., 2020). PTSD comorbidities such as alcohol and drug abuse,
borderline personality disorders (BPD), and eating disorders were also found to be more
common in adults who experienced adverse childhood experiences (Sheffler et al., 2020).
According to Sheffler et al. (2020), a study conducted in 2016 found that there is a dose-response
association between an individual’s eating disorder severity and the number of adverse childhood
experiences (ACEs) they have experienced. Research has demonstrated that a history of trauma

48
during childhood increases the likelihood of developing sleep disorders such as narcolepsy and
insomnia (Harris, 2018). Although ACEs primarily affect mental and physical health, they can
have far-reaching effects on a person’s quality of life (Stinson et al., 2016).
ACEs and Crime
Extensive connections have been established between experiencing early hardships and
engaging in criminal and/or violent behavior. According to Waite and Ryan (2019), children who
have experienced adverse childhood experiences (ACEs) are twice or four times more likely to
participate in criminal activity when they are young adults. There is a 53% increase in the
likelihood of juvenile arrests, a 38% increase in the likelihood of adult arrests, and a 38%
increased likelihood of arrests for violent crimes for children who have experienced neglect
and/or abuse (Stinson et al., 2016). Multiple forms of stress raise the risk of violent and criminal
conduct (Baglivio et al., 2020). Furthermore, compared to children from wealthier
socioeconomic backgrounds, neglected and disadvantaged youth had a higher likelihood of being
involved in criminal activity (Stinson et al., 2016). Individuals with a prior experience of
childhood adversity have a higher incidence of criminal behavior among the mentally ill (Stinson
et al., 2016).
Research conducted by Baglivio et al. (2020) has demonstrated that individuals in the
juvenile justice system who have received the most severe placements tend to have a greater
number of Adverse Childhood Experiences (ACEs) compared to others. Research conducted by
Baglivio et al. (2020) has demonstrated that for every extra Adverse Childhood Experience
(ACE) encountered before the age of 12, there is a 20% increased likelihood that the individual
will be placed in a residential facility by the time they reach 18 years old. The research
demonstrated that individuals who are significant, violent, and repeat offenders are more likely

49
to have suffered adverse childhood experiences (ACEs) (Baglivio et al., 2020). In contrast,
individuals who have committed less serious or less violent crimes, as well as those who have
not offended, have encountered less or no adverse childhood experiences (Baglivio et al., 2020).
According to Baglivio et al. (2020), data from the Cambridge Study in Delinquent Development
(CSDD) conducted in 2017 showed a positive correlation between the ACE score and the
number of crimes from ages 10 to 56. Recent research has indicated a potential correlation
between adverse childhood experiences (ACEs) and the probability of being involved in gang
activities (Moss et al., 2020).
Those who have experienced adverse childhood experiences (ACEs) are more likely to
engage in violent behavior if they fear academic limits or an early death. A sense of hopelessness
and “nothing to lose” is common among youth who have grown up in violent communities
because they internalize the message that they will die young (Brumley et al., 2017). Brumley et
al. (2017) found that they engage in more criminal, violent, and problematic behavioral patterns.
Young adults who have experienced adverse childhood experiences (ACEs) have led them to
develop a belief that they have no power over their lives and future opportunities (Brumley et al.,
2017). Furthermore, they may also recognize that their limited resources and lack of support will
provide challenges in pursuing their future aspirations (Brumley et al., 2017). Individuals who
have experienced childhood abuse are more likely to engage in violent behavior (Stinson et al.,
2016).
ACEs and Relationships
Those who have gone through traumatic experiences often find it challenging to function
socially (van der Kolk, 2014). According to van der Kolk (2014), individuals who have
experienced trauma get trapped in a state of survival, causing them to prioritize fighting and

50
neglecting the need for love, care, and nurturing. People who have experienced trauma at the
hands of an adult they trusted often struggle with attachment issues (Statman-Weil, 2016).
Furthermore, these people have trouble forming meaningful relationships and tend to keep others
at arm’s length as a defense mechanism. Sheffler et al. (2020) found that individuals who
experienced early adversity generally have faulty coping mechanisms, which can manifest in
interpersonal difficulties. An underlying cause of this dysfunction is that individuals who have
experienced abuse from their caregivers come to realize that they lack the ability to influence or
manage the events that occur to them. This damages their internal locus of control, which is
crucial for the development of successful coping strategies (van der Kolk, 2014). These adults
frequently experience stress by either dissociating (flight) or becoming unpredictable and
aggressive (fight), which affects their interpersonal connections (van der Kolk, 2014). According
to Doyle and Cicchetti (2017), adults who were maltreated throughout their childhood tend to
exhibit heightened sensitivity, hostility, and aggression in their relationships, along with low
self-esteem. Adult connections, including friendships, romantic partnerships, and parent-child
relationships, are severely impacted by these features (Doyle & Cicchetti, 2017). Nevertheless,
the influence of parents' adverse childhood experiences (ACEs) on their children might extend
beyond the current parent-child connection and have detrimental effects on future generations
(van der Kolk, 2014).
ACE’s and Intergenerational Trauma
The reality that adverse childhood experiences (ACEs) frequently impact subsequent
generations of the same family is one of the most discouraging parts of ACEs (Steele et al.,
2016). As children grow into adults, the effects of childhood hardship can shape their adult lives,
including their parenting styles and the dynamics within their families (Steele et al., 2016).

51
Research on attachment theory that spans more than half a century has demonstrated. That
parents’ treatment of their own children is shaped by their own early experiences (Steele et al.,
2016). Simply said, adults model their parenting styles after their own formative experiences;
hence, a history of physical or emotional violence in infancy increases the likelihood that an
abusive parent will raise their own children violently (Steele et al., 2016). There is a pattern that
demonstrates how mistreated children are more likely to engage in violent behavior as adults
(Steele et al., 2016). Kuffer et al. (2016) discovered that children of indentured servants reported
higher levels of physical, emotional, and neglect compared to their peers born to non-indentured
servant parents in a 1970s Swiss study. According to Kuffer et al. (2016), these parents passed
on the negative effects of their difficult childhood experiences to their own children. Hardcastle
et al. (2018) observed that intergenerational cycles of adverse childhood experiences (ACEs) can
persist over extended periods, trapping subsequent generations in poverty. Parents who had a
history of adverse childhood experiences (ACEs) frequently found themselves in a difficult
financial situation as adults, which was a factor that frequently drove them to mistreat and
neglect their own children (Kuffer et al., 2016). There is a correlation between parental stress and
the way they interact with their children, and this stress is frequently triggered by the parent’s
own adverse childhood experiences (ACEs) (Steele et al., 2016). The painful consequences of
adverse childhood experiences are further exacerbated by their ability to be passed on throughout
generations, creating a cycle of abuse. Therefore, it is imperative to discover strategies to
alleviate these impacts and prevent the cycle of abuse.
Resilience
Resilience is the capacity to overcome adversity, whether they be personal, familial, or
communal (Masten, 2018). Research conducted by Southwick et al. (2014) suggests that

52
resilience may be a greater phenomenon than was previously thought. The defensive factors of
resilience must be understood to deal with problems (Masten, 2018). The subsequent part will
examine the body of knowledge pertaining to resilience and its correlation with ACEs.
Norman Garmezy and Michael Rutter established the resilience theory, which focuses on
the study of stress and coping in children (Masten, 2018). During the 1950s, 1960s, and 1970s,
there was a plethora of research on high-risk populations, children’s personality traits, and the
significance of how individuals dealt with challenges (Masten, 2018). This was considering the
extensive problems experienced in the first half of the twentieth century, including the Great
Depression and World Wars I and II (Masten, 2018). These studies played a crucial role in the
early stages of resilience research, since they were essential for understanding the different ways
in which individuals react to stress, which is a fundamental aspect of the resilience theory
(Masten, 2018). According to Heard-Garris et al. (2018), resilience is influenced by three
specific factors: one’s autonomy and self-esteem, the quality of one’s family ties, and the
availability of external support networks that promote coping. The frequency and severity of
stress episodes themselves may be less significant than an individual’s capacity to manage stress,
which may be more significant for their overall morale, social functioning, and health/illness
(Heard-Garris et al., 2018).
The Garmezy and Rutter (1983) study examined protective mechanisms as variables that
influence an individual’s capacity to cope or demonstrate resilience (Heard-Garris et al., 2018).
Heard-Garris et al. (2018) define coping as the process of resolving problems through realistic
and adaptable thoughts and actions, thereby reducing tension. The two goals of coping
mechanisms are problem-solving and emotional regulation (Southwick et al., 2014). These
mechanisms are factors in a person’s life that serve to protect them from harm caused by risk

53
factors (Southwick et al., 2014). A resilient person has a good attitude and/or strong sense of self,
lives in a supportive household, and has access to a network of friends and family (Southwick et
al., 2014).
Researchers argue that caregiver conduct can have either a negative impact or a
protective effect on children’s development. During critical stages of neuroplasticity in human
development, the presence of protective variables, such as effective parenting and self-regulation
abilities, has a significant impact on an individual’s capacity to adjust and cope (Masten, 2016).
Therefore, the ability to overcomeOadversity, known as resilience, can be shaped by cultural
elements such as family members, peer support, and faith-based beliefs (Masten, 2016). These
factors serve as external protective influences within a person’s mesosystem, ecosystem,
macrosystem, or chronosystem (Masten, 2016). Although much progress has been made in
understanding the impact of unfavorable events on the development of the mind and body, there
is still limited knowledge regarding the adaptive experiences that might mitigate the effects of
ACEsO(Masten, 2016).
Heard-Garris et al. (2018) looked at the connection between resilience and cognitive
interpretations of children, taking a look at how cognition, an intrinsic component of the 40
microsystems, is related to resilience. Resilience was described by the researchers as the capacity
to remain mentally and socially healthy in the face of continuous adverse challenges (Heard-
Garris et al., 2018). Researchers in a South African area experiencing socioeconomic hardship
interviewed 1,025 school-aged children (ranging from fourth to sixth grade) (Heard-Garris et al.,
2018). To investigate how students’ mental health and their impressions of their school were
reflected in their cognitive interpretations, researchers utilized an array of tests, which include
the Cognitive Triad Inventory for Children (CTI-C) and trauma and behavior questionnaires

54
(Heard-Garris et al., 2018). The results were consistent with prior research, showing that higher
psychological functioning was exhibited by respondents who had more positive cognitive
interpretations (Heard-Garris et al., 2018). This study shows that how kids think about events
and the world around them might affect how they feel about themselves, how they see school,
their goals for the future, and how they interact with others (Heard-Garris et al., 2018). Mood,
somatization, and traumatic event-related psychological functioning are all positively correlated
with cognitive interpretation (Heard-Garris et al., 2018). Therefore, one of the main variables
affecting resilience is cognitive interpretation.
A study conducted by Heard-Garris et al. (2018) found that resilience is linked to
characteristics at the child, family, and community levels. Heard-Garris et al. (2018) looked at
characteristics related to resilience in children at the individual, family, and community levels
using data from the National Survey of Children’s Health 2011–2012. They found that ACEs
influenced parents’ perceptions of their children’s resilience. The results showed that 32.6% of
parents believed that their child was not displaying resilience, whereas 67.4% believed that their
child was displaying resiliency (Heard-Garris et al., 2018). According to Heard-Garris et al.
(2018), there is a negative correlation between the number of ACEs and the likelihood of parents
perceiving resilience. The study conducted by Heard-Garris et al. (2018) identified several
family variables that promote resilience, which include attending religious services together,
communicating thoughts with the child, and sharing meals as a family. Furthermore, the study
revealed that community-level characteristics, such as the level of cohesion among neighbors,
the overall safety of the neighborhood, and the availability of amenities, were identified as
significant contributors to resilience (Heard-Garris et al., 2018). Evidence suggests that
individuals who have been exposed to Adverse Childhood Experiences (ACEs) may also possess

55
the ability to overcome adversity andOdemonstrate resilience (Heard-Garris et al., 2018).
While protective mechanisms help people become more resilient, two concepts that can
undermine resilience are risk mechanisms and vulnerability (Southwick et al., 2014). The risk
mechanisms are an individual’s level of resilience that can be influenced by the quantity of risk
variables they encounter, especially if there are numerous risk mechanisms and little or no
protection mechanisms (Southwick et al., 2014). Another crucial concept in the research of
resilience is interaction effects. These consequences can influence a person’s life trajectory in
ways that go beyond autonomy, self-worth, family dynamics, and outside support networks
(Southwick et al., 2014). Numerous interaction effects and their consequences on resilience have
been studied. It is imperative that all researchers investigating resilience’s role and the factors
impacting its development acknowledge these interaction effects: (1) gender, suggesting that
boys are more vulnerable to negative emotional effects from family discord; (2) temperament,
suggesting that children with negative traits were more likely to elicit critical reactions from
parents; (3) at least one good parent-child relationship, which reduced the risk of psychiatric
problems; and (4) marital planning and support (Southwick et al., 2014).
Contemporary resilience theorists agree that an individual’s level of resilience is mostly
determined by their response to adversity, regardless of the presence or absence of protective and
risk mechanisms (Southwick et al., 2014). Heard-Garris et al. (2018) emphasize the importance
of considering individual variations in how people respond to adversity, rather than assuming
that outcomes can be explained solely by the interplay between positive and negative influences,
which are assumed to affect everyone in a uniform manner and to the same extent. According to
Southwick et al. (2014), resilience has a distinct significance for every person, family, or culture
affected by adversity. They highlight that individuals may exhibit greater resilience in certain

56
areas of their lives compared to others and throughout specific periods of their lives compared to
others (Southwick et al., 2014). Nevertheless, scholars acknowledge that a child’s ability to build
resilience depends on having healthy interactions in their family and society (Southwick et al.,
2014). The presence of social skills is crucial for fostering positive interactions, as they elicit
favorable responses from others. Furthermore, it is imperative that the key adult figures in these
individuals’ lives, such as family members and educators, demonstrate a willingness to
comprehend the individuals’ experiences and provide them with unwavering support (van Breda,
2018). A child’s development of resilience is dependent on several key traits, including a healthy
attachment relationship, good caregiving, emotion regulation skills, self-awareness, the ability to
visualize the future, and a motivation system that drives learning, growth, and adaptation to the
environment (Southwick et al., 2014).
Heard-Garris et al. (2018) shares that the nature of the connection between risk
mechanisms and resilience is complicated. Risk and stress can have a steeling effect, which
makes certain people stronger because they learn to persevere in the face of hardship (Heard-
Garris et al., 2018). In contrast, van Breda (2018) claimed that individuals who face persistent
adversity may initially possess resilience, but their capacity to demonstrate resilience diminishes
over time as each traumatic encounter depletes their available resources. According to the
resilience theory, both external risk factors and internal responses to traumaOinfluence a person’s
life path. Although the existence of protective variables can create a more favorable setting for
the growth of resilience, it is the individual's reaction to those protective circumstances that
ultimately defines their level of resilience. According to Southwick et al. (2014), it’s critical to
consider how specific characteristics, general processes, comprehension and recognition of
participants’ resilience, coping strategies, and vulnerability, along with the beneficial elements or

57
interaction effects in their lives, play a role in resilience.
Resilience and Its Function in Overcoming ACEs
The capacity to overcome adversity is crucial for overcoming childhood trauma and
avoiding the long-term effects of adverse childhood experiences (ACEs) (Bellis et al., 2018;
Heard-Garris et al., 2018; Sciaraffa et al., 2018). The characteristics associated with resilience
include traits such as determination, self-efficacy, emotional and cognitive control under difficult
circumstances, adaptability, capacity to endure negative emotions, and dedication to attaining
objectives (Poole et al., 2018). According to Oshri et al. (2019), resilience is not something you
are born with but something you work on developing. Many studies In the field of resilience seek
to clarify the elements that shape people’s reactions to hardship and the ways in which
professionals who assist victims of adverse childhood experiences (ACEs) can foster resilience
in those individuals (Heard-Garris et al., 2018; Woods-Jaeger et al., 2018).
Resilience Development
Resilience development is influenced by both internal and external variables (Heard-
Garris et al., 2018). Resilience is characterized by certain personal qualities such as
independence, positive outlook, self-control, belief in one’s abilities, and overall well-rounded
development of interpersonal and psychological skills (Bellis et al., 2018). Resilience is
enhanced by developing problem-solving skills and the ability to learn from failures (Bellis et al.,
2018). A recent study conducted by Hamby et al. (2020) found that among young individuals
who have experienced many Adverse Childhood Experiences (ACEs), possessing a sense of
purpose plays a crucial role in developing resilience. They can feel purposeful when they are a
part of something bigger than themselves (Hamby et al., 2020).

58
The external elements that contribute to the development of resilience can be classified
into two distinct categories: strong familial connections and a dependable network of support
beyond the immediate family (Bellis et al., 2018). Close relationships with parents and
caregivers, parents’ stress-management skills, and a sense of belonging and/or attachment are all
part of the first group (Crouch et al., 2019). The second group consists of many identified
components that foster resilience, such as social networks, role models, educational
opportunities, and cultural norms and values (Crouch et al., 2019). The presence of a buffering
adult to sufficiently lessen the impact of the stressor is essential to prevent a manageable stress
response from overflowing into the toxic stress zone (Nadine Burke Harris, 2018). Moreover,
children who have dependable parents who provide them with strength and comfort throughout
their lives have an advantage that acts as a form of defense against any adverse circumstances
they may encounter (van der Kolk, 2014).
A stable adult figure throughout a child's formative years might provide a safe haven
away from the cumulative trauma of adverse childhood experiences (Bellis et al., 2018). In a
study conducted by Crouch et al. (2019), it was discovered that individuals who reported
experiencing four or more Adverse Childhood Experiences (ACEs) benefited more in terms of
their psychological and physical well-being in the future if they had an adult figure in their
childhood that not only fulfilled their basic requirements but also provided them with a sense of
safety. According to Hardcastle et al. (2018), resilience studies emphasize the significance of
receiving ongoing support from a reliable adult to reduce the impact of adverse childhood
experiences (ACEs). Although it is often associated with a parent or relative, the potential
function of an educator should also be taken into account. Prior research has demonstrated that
establishing positive teacher relationships can serve as a protective factor against emotional and

59
behavioral issues in individuals who have experienced abuse and neglect (Bellis et al., 2018;
Crouch et al., 2019). Having a community of support in place is crucial for trauma survivors to
overcome challenges (Walsh et al., 2019b).
It is impossible to overstate the significance of social support in developing resilience.
Teens who have healthy families are less likely to drink and use drugs, have more involvement
in extracurricular activities, and report better mental health overall (Walsh et al., 2019). Having
strong social networks is just as crucial as having supportive familial relationships. According to
Dr. Bessel van der Kolk, social support is the most effective defense against being overcome by
stress and trauma, as evidenced by countless research studies conducted on disaster response
worldwide. According to van der Kolk (2014), the most crucial aspect is the reciprocity factor.
Victims of trauma can rehabilitate in a safe atmosphere when they know that someone is
genuinely paying attention to them and caring about their well-being. Bellis et al. (2018)
emphasized the importance of positive role models, creating opportunities for networking and
friendship building, and treating children fairly and equitably. These factors not only improve
childhood but may also play a crucial role in their health and school attendance. Evidence
suggests that children who experience adversity require the assistance and motivation of
individuals, such as parents, other family members, or adults from their community, in order to
develop resilience (van der Kolk, 2014).
Research Informed Intervention and Prevention
There has been some progress in understanding how to intervene and avoid problems in
order to increase resilience. In a narrative analysis of 20 research studies, Moeller-Saxone et al.
(2014) found that survivors of child maltreatment (CM) and intimate partner violence (IPV) were
more likely to be resilient. The results showed that there is a lack of research that takes resilience

60
into account when trying to determine what makes people resilient and how to improve resilience
through the use of targeted resilience measures (Moeller-Saxone et al., 2014). Nevertheless, a
number of qualitative studies have shown solid evidence in favor of resilience-promoting
preventative interventions, including drug addiction programs, home visits for moms at risk, and
a methadone program for women (Moeller-Saxone et al., 2014). Furthermore, Moeller-Saxone et
al. (2014)Odiscovered that cognitive restructuring was successful in decreasing stress and
symptoms in survivors of intimate partner violence (IPV). Among indigenous communities and
low- and middle-income nations, women who become village health workers reported less
discrimination, more civic and social participation, and an increase in their concept of
independence (Moeller-Saxone et al., 2014).
Summary
The literature review explored the resilience theory as the foundation for this hermeneutic
phenomenological study exploring how individuals who have experienced ACEs are able to
develop resilience. Resilience is the capacity of an individual to adjust and respond effectively to
challenging situations or potential harm (Masten, 2018). Having a strong sense of autonomy,
having supportive familial relationships, and having access to outside support networks to help
with coping are three protective variables that are crucial for fostering resilience (Bethell et al.,
2017). The literature review examined a wide range of subjects that were pertinent to ACEs and
resilience. Adults’ experiences with ACEs and associated health outcomes were initially
documented in the Adverse Childhood Experiences (ACE) research conducted by Felitti et al.
(1998) (Crouch et al., 2019). The literature on maltreatment in early life was examined, with a
focus on the development of the adverse childhood experiences (ACE) concept (Crouch et al.,
2019). This section examines the prevalence and scientifically proven connections between

61
adverse childhood experiences (ACEs) and detrimental impacts on physical, mental, and
emotional health in adulthood. It also highlights certain favorable outcomes that can intensify the
impact of ACEs. It established how the detrimental effects of ACEs during childhood interact
with victims’ neurological, social, emotional, and psychological growth throughout time, laying
the groundwo’k for becoming resilient in adulthood. Furthermore, research has demonstrated
that individuals who have experienced adverse childhood experiences (ACE) are more prone to
engaging in criminal and violent behavior (Baglivio et al., 2020; Brumley et al., 2017). There is
evidence in the literature that adverse childhood experiences (ACEs) can affect generations
(Hardcastle et al., 2018). The effects of childhood adversity extend beyond the individual who
endures it (Hardcastle et al., 2018).
Furthermore, this chapter examined the correlation between resilience and the ability to
overcome childhood trauma; additionally, they have explored strategies for developing resiliency
(Bellis et al., 2018). According to research, a number of factors are essential to developing
resilience, including optimism, autonomy, the capacity to learn from mistakes, a sense of
belonging, solid family ties, and outside support networks (Crandall et al., 2019; Heard-Garris et
al., 2018). The most significant benefit for those who have experienced childhood trauma is
having a supportive adult there to help them cope with the stress caused by adversity (Bellis et
al., 2018; van der Kolk, 2014).
According to the study’s findings, which affected nearly two-thirds of the sampled
population, ACEs were more common than previously believed (Crouch et al., 2019; Felitti et
al., 1998). TheOtopic of adverse childhood experiences (ACEs), as well as the impact of
childhood trauma, was brought toOthe forefront of the minds of professionals in the fields of
medicine, education, social work, and psychology (Crouch et al., 2019). Although there are

62
numerous studies on childhood trauma and its effects on different stages of life, as well as the
importance of resilience in overcoming trauma, there is a lack of research on lived experiences of
resilience and adverse childhood experiences. To fill the gap in literature, this qualitative study
will explore the lived experiences of individuals who have experienced adverse childhood
experiences in the Pacific Northwest to gain insightOinto their perspectives regarding the factors
that have contributed to or facilitated their resilience. These factors may include personal
characteristics, coping mechanisms, stress response, resources utilized to address adverse
childhood experiences (ACEs), and relationships. It is important to conduct research on
resilience in order to assist researchers in comprehending the roles that contributing factors play
and in developing therapeutic techniques that can reduce the negative effects of adverse
childhood experiences (ACEs).

63
Chapter Three: Methods
Overview
The purpose of this hermeneutic phenomenological study was to explore the firsthand
livedOexperiences of individuals in the Pacific Northwest who have high levels of Adverse
Childhood Experiences (ACEs) and have demonstrated resilience. Several studies primarily
examine Adverse Childhood Experiences (ACEs) and resilience using a quantitative approach to
investigate symptoms and treatment results. The body of literature devoted to survivors’ actual
experiences is either nonexistent or out of date. This study explored the lived experiences of
individuals who have experienced adverse childhood experiences (ACEs) and their ability to
adapt and recover in adulthood. This study learned about the lived experiences of the participants
over the course of their lives, including their perceptions, difficulties, relationships with family
and friends, social support, resources, spirituality, and coping methods. The findings of this study
offerOpractical information to help break down barriers around trauma discussions, encourage
individuals to communicate their needs and struggles to their healthcare providers, and present
strategies for mental health interventions with victims of adverse childhood experiences (ACEs).
The research design, including the study type, design details,Othe rationale behind design choices,
and research questionsOis covered in this chapter. In addition, this chapter addresses the methods
usedOfor participant screening and selection, the rationale behind picking this particular
demographic, and the target population. Furthermore, the research methods and sample size are
discussed in detail.
Design
This is a qualitative phenomenological study. This qualitative study was selected to
describe the lived experiences of individuals who have successfully overcome Adverse

64
Childhood Experiences (ACEs) and demonstrated resilience in adulthood. According to Merriam
and Tisdell (2016), qualitative research is intended to investigate the concepts, opinions, or
experiences of individuals, while quantitative research uses statistics to quantify, measure, and
analyze data. The study employed a hermeneutic phenomenological design to explore and
document the lived experiences of participants who endured childhood trauma and subsequently
developed resilience in adulthood. This approach allowed for an in-depth examination of the
participants’ personal narratives, focusing on their traumatic experiences during childhood and
the subsequent journey towards becoming resilient adults. By utilizing this qualitative
methodology, the research uncovered the essence of the resilience-building process and gained
insights into the complex interplay between adversity and positive adaptation over time.
A phenomenological study captured the personal experiences of individuals and helped
understand how these experiences affect, shape, and transform their perception of themselves
and their lives (Merriam & Tisdell, 2016). Phenomenology utilizes the concept that there is a
commonality in all human experiences and that it is feasible to captureOthe shared experiences of
the phenomenonO(Miles et al., 2020). Phenomenological methods can be used to find, study, and
understand the core of a shared experience. This hermeneutic phenomenological research study
examinedOthe lived experiences of those who have overcome childhood trauma and the
phenomena of resilience in relation to adverse childhood experiences (Miles et al., 2020). This
study identifiedOhow the phenomenon of resilience is experienced in adulthood and found the
commonalities across a group of individuals who experienced similar adverse childhood
experiences.
A hermeneutic approach was chosen for this phenomenological study because the goal is
to understandOthe participants’ experiences (phenomenological) and to make sense of those

65
experiences and give them meaning (hermeneutical). According to Creswell and Poth (2018), the
characteristics of qualitative research include the clarification of the occurrence of social
phenomena, the comprehension of various aspects of the world, the provision of answers to
questions concerning behavior and opinions, the identification of the role that social influence
plays, and the comprehension of the reasons behind the occurrence of things. Using the
researcher’s own experiences as an instrument, conducting interviews, focus groups,
observations, and member checks are all examples of data collection methods used to triangulate
information in qualitative research, which is relevant to this study (Creswell & Poth, 2018).
Creswell and Poth (2018) identified the following qualitative research attributes that were
implemented in this study: Concentrate on one social phenomenon or learn to see the world
through the eyes of someone who overcame early interpersonal trauma. Provide responses to
questions concerning the effects of forgiveness on the recurrence of trauma symptoms and the
reasons why some people can overcome these symptoms as they grow older. During the
interviews, ask open-ended questions to help people talk freely about their experiences. For
triangulation, I used a variety of data-gathering techniques. Relationship difficulties persist
throughout adulthood for many people who have survived interpersonal childhood trauma. The
individual may find it difficult to move past their childhood experiences, which can leave them
emotionally and functionally attached to the perpetrator(s) and make it difficult for them to live
their life to the fullest (Schlumpf et al., 2021). Therefore, the purpose of this qualitative study
was to understand how individuals with adverse childhood experiences are able to move forward
with their lives with the ability to forgive and develop resilience in adulthood (Merriam &
Tisdell, 2016).

66
Phenomenological Research Design
According to Merriam and Tisdell (2016), there are numerous varieties of qualitative
research, such as case studies, ethnography, grounded theory, and phenomenology. In social
experience, phenomenological research provides an explanation for a phenomenon or lived event
(Creswell & Poth, 2018). Phenomenological research is used to explain what a person hasObeen
through from their own point of view (Creswell & Poth, 2018). According to Laverty (2003),
Husserl introduced the phenomenological research approach in the early 1900s to study the core
elements of human experience. The purpose of phenomenological research has become clearer
over time. The goal of phenomenology is to comprehend, while quantitative research is to
explain, evaluate, or quantify (Sloan & Bowe, 2014). The phenomenology design was selected
for this study due to its objective of comprehending the experiences of survivors of ACEs and
the role that resilience plays in their lives.
Hermeneutic Phenomenological Design
According to Sloan and Bowe (2014), hermeneutical phenomenology seeks to provide a
comprehensive account of the lived experience, recognizing that human experiences are
complicated and cannot be articulated concretely. Phenomenological hermeneutics focuses on
our active involvement in understanding the meaning of events as it develops throughout time
(Laverty, 2003). In contrast to other methodologies, the hermeneutic approach is distinguished
by its ability to offer a perceptive account of human experience without the need for labeling,
categorization, or conceptualization (Laverty, 2003). The purpose of the hermeneutic approach
was to bring attention to the significance and value of the ordinary, insignificant things that make
up our lives (Laverty, 2003). In addition, the objective was to understand that human experience
and consciousness are interconnected and that it is impossible to separate the twoO(Creswell &

67
Poth, 2018). Laverty (2003) defines lived experience as an experience without conclusions.
However, meaning is only obtained when it is expressed in a specific manner.
Laverty (2003) discussed the meaning of lived experience through the use of concrete
reflection and storytelling. Additionally, they stated that the experience itself lacks significance.
Understanding and meaning are created from the experience when it is recalled and used to assist
another person in understanding their experience (Laverty, 2003). The phenomenon of resilience
and adverse childhood experiences are interpreted in this study, and the meaning of these
phenomena is derived from personal accounts or actual individual experiences. Although
alternative approaches may offer valuable insights into the connection between these events, the
objective of this study was to gainOunderstanding of the event through the narrative and
perspective. The most effective way to accomplish this objective is through the application of
hermeneutic phenomenology. This design facilitates the exploration of the development of
resilience following adverse childhood experiences and the potential advantages that can be
gained from cultivating resilience.
Research Questions
Research Question 1
Research question one asks, “How do adults who experienced childhood trauma describe
the essence of their lived experiences?” The resilience theory states that specific personality
traits, strong social networks, the ability to overcome adversity, and positive relationships are the
main components of resilience (Masten, 2018). The researcher looked for commonalities of
personality, social networks, and intrapersonal relationships in life that helped overcome
adversity and develop resilience (van Breda, 2018).

68
Sub-question 1
Sub-question one asks, “What are the perceived long-term effects of childhood trauma on
the lives of adults, as revealed through their firsthand accounts and reflections?” Research has
demonstrated that traumatic experiences in childhood can lead to negativity and a lack of faith in
one's own abilities to overcome adversity (Masten, 2018). The researcher looked for common
themes during adolescence and adulthood that help individuals overcome these limitations,
cultivate resilience, and become productive members of society (van Breda, 2018).
Sub-question 2
Sub-question two asks, “How do adults who experienced childhood trauma describe how
their experiences have shaped their understanding of themselves and their world?” The life
experiences of study participants, both positive and negative, will be considered as they recount
the events that have molded their identities (Masten, 2018). The participants were requested to
reflect on the experiences that they had throughout their adult lives up to this point and describe
which experiences made a significant contribution to their achievement (van Breda, 2018). For
the purpose of the study, the researcher looked for common themes, which will be supplied with
the data (van Breda, 2018).
Setting
Creswell and Poth (2018) stated that participants in phenomenological studies do not
have to be in one physical location. Instead, they should be individuals who have personally
encountered the phenomenon being studied and are able to describe their own firsthand
experiences. This study was conducted entirely online, with participants recruited from the
Pacific Northwest region. This approach aligns with the growing trend of online therapy and
research, demonstrating the feasibility of conducting such studies in virtual environments. All

69
interviews were conducted using the Zoom platform, eliminating the need for a specific physical
location or setting. Participant recruitment was carried out through Facebook and relevant
Facebook groups. The study targeted online communities and groups that were already engaged
in discussions related to mental health, particularly trauma. This strategic approach served two
purposes: firstly, it ensured that participants met the study's inclusion criteria, and secondly, it
provided a supportive environment to minimize potential harm associated with discussing
traumatic experiences. To protect the privacy and confidentiality of the participants, pseudonyms
were used throughout the study. This measure ensured that each participant's identity was
safeguarded while allowing for the collection of rich, detailed data about their lived experiences.
This methodology allowed for a diverse group of participants from across the Pacific Northwest
to share their experiences with childhood trauma and resilience, providing valuable insights into
the phenomenon without the constraints of geographical proximity.
Participants
This section discusses the sample size, sample type, sample pool, and sampling processes
used to conduct this study. The demographic data I obtained included age, gender, and
race/ethnicity. The study outlines the criteria for including or excluding people and describes the
methods used to evaluate and select participants.
Sample
According to Creswell and Poth (2018), qualitative research typically employs a sample
size ranging from five to twenty-five participants. For this study, the desired sample size was set
at 10 individuals, as it was considered unlikely to reach saturation with only 5 samples (Merriam
& Tisdell, 2016). Conducting 10 participant interviews was intended to ensure that the issues
being discussed were thoroughly addressed and reached a point of saturation. However, this

70
study was only able to recruit 8 participants. The study utilized purposive sampling to select
participants who met the specific criterion of having experienced childhood trauma (Creswell &
Poth, 2018). The target demographic was individuals aged 26 and older, corresponding to middle
adulthood (Creswell & Poth, 2018). To participate in the study, individuals were required to have
access to the necessary technology and be able to use it without restriction. Those who failed to
meet these specified requirements were excluded from participation. For safety considerations,
individuals who presented mental health challenges were not allowed to participate in the study
(Creswell & Poth, 2018). This precaution was taken to ensure the well-being of all participants
and the integrity of the research process.
Participants wereOrecruited using convenience sampling. I used preexisting groups to find
potential participants, and I conducted preliminary screenings using Survey Monkey (Merriam &
Tisdell, 2016). Participants who passed the preliminary screening were invited to take part in the
study. One participant was recruited through the technique of snowball sampling, which involved
asking initial participants to get in touch with others they may know who could be interested in
taking part in this study (Merriam & Tisdell, 2016). The invitation post contained the study's
objective and a detailed explanation of the criteria for including or excluding participants
(Creswell & Poth, 2018). Participants were required to self-verify their eligibility based on the
requirements. This criterion was verbally confirmed prior to conducting an interview.
Furthermore, each participant selected was given a pseudonym to protect their identity (Creswell
& Poth, 2018). Each individual was given the opportunity to discuss this during the verbal
consent procedure during the interview. Participants had the option to select their pseudonyms
(Merriam & Tisdell, 2016).
To facilitate the process, consent and confidentiality information, respondent

71
demographic data, the original ACEsOStudy Questionnaire (ACESQ) (Felitti et al., 1998a), and
the Five-by-Five Resilience Scale (5x5RS) were incorporated into an online screening profile
(Radcliff et al., 2019). I created it using SurveyMonkey.com. The screening profile started with
permission information so that people who want to take part in the study know what it involves,
what kinds of questions will be asked, and what risks are involved (Creswell & Poth, 2018). I put
a link on the screening page so that participants can get the consent information and study details
and save a copy of them.
The screening profile asked for information about the person's age, gender, race or
ethnicity, level of education, job, zip code, and bestOway to be contacted, along with contact
information (Creswell & Poth, 2018). I set up the screening profile so that personal information
and less bothersome questions come up first. Participants in the study had an ACESQ score of 4
or more or one ongoing ACE, a 5x5RS score in the top two quartiles, and have lived in the
Pacific Northwest for at least 10 years. This is because parts of the study are about the
availability and access to resources that helped individuals become resilient in adulthood. Not
being younger than 26 or having not lived in the Pacific Northwest for ten years or more are
some of the demographic requirements that ended the online screening process right away. The
final "thank you" page of the screening profile automatically appeared. The screening was
implementedOso that people wouldn't have to answer intrusive questions if they did not qualify
for the study.
The Adverse Childhood Experiences (ACE) Questionnaire is a self-reporting measure
designed to assess experiences related to abuse, neglect, and household dysfunction during
childhood. It consists of 10 items that require simple yes or no responses from participants.
While the original ACE questionnaire remains widely used, researchers have developed

72
expanded and improved versions to capture a broader range of adverse childhood experiences.
These newer questionnaires aim to provide a more comprehensive assessment of childhood
adversity. However, it's important to note that the validity and reliability of these expanded
versions have not yet been fully established. Finkelhor et al. (2015) addressed this issue in their
research, suggesting that additional testing is necessary to confirm the suitability of new items
included in the Adverse Childhood Experiences Inventory—Revised. This expanded inventory
introduces new categories of adverse experiences, but its effectiveness within the context of the
original ACE scale setting requires further validation. As research in this field continues to
evolve, it remains crucial to balance the desire for more comprehensive assessments with the
need for validated, reliable measurement tools. The ongoing refinement of ACE questionnaires
reflects the growing understanding of the complex nature of childhood adversity and its long-
term impacts. Based on prior research, the ACESQ is the preferred questionnaire because of its
validity and reliability (Merrick et al., 2018; Sacks et al., 2014).
The 5x5RS utilizes a self-report approach and consists of 25 Likert scale questions
designed to evaluate adaptability, emotion control, optimism, self-efficacy, and social support
(Felitti et al., 1998a). Responses exhibit a spectrum of accuracy, fluctuating between
significantly inaccurate and exceptionally accurate. De Simone et al. (2018) conducted an
evaluation of the 5x5RS's reliability, convergent validity, factor structure, and criterion-related
validity using two samples (n = 475 and n = 613). The study indicated that the 5x5RS
demonstrates a robust level of internal consistency (De Simone et al., 2018). This is also
associated with the Connor-Davidson Resilience Scale (CD-RISC), a widely utilized assessment
of resilience (De Simone et al., 2018). Furthermore, the 5x5RS is capable of precisely evaluating
individuals exhibiting resilience traits that fall within one standard deviation of the mean.

73
Compared to earlier resilience scales, the 5x5RS integrates both internal and external protective
factors that have been shown to affect a person's resilience level (De Simone et al., 2018). De
Simone et al. (2018) found evidence indicating that individuals who score high on a resilience
measure might not actually encounter fewer life stressors. Nonetheless, their responses differ
from those of other individuals.
Inclusion Criteria
The study involved a sample of middle-aged individuals who have been victimized by
childhoodOtrauma committed by a family member or a trusted adult. Adults in positions of trust
or power over a child may fall into this category, as can coaches, instructors, neighbors, friends,
or family. This excludes individuals who are unfamiliar or have had brief encounters with the
individual during their childhood (Creswell & Poth, 2018). In order to ensure the integrity of this
study and minimize potential distress, participants were exclusively chosen because of their
previous involvement in counseling, and they were willing to openly describe their childhood
experiences. The purpose of this was to reduce the intense discomfort that may arise from
revealing abuse during childhood for the first time or discussing issues that still bring discomfort
to the person (Creswell & Poth, 2018).
The target population consisted of adults aged 26 or older. The purpose of selecting this
range is to include individuals who are no longer vulnerable to the abuse of those who may have
harmed them in their childhood. It also allows for a sufficient amount of time for these
individuals to begin coping with the trauma they have experienced (Creswell & Poth, 2018).
Additionally, this range included individuals who may be more receptive to considering different
perspectives and ideas related to trauma and resilience. The aim is to expand our understanding
of how childhood trauma affects the process of healing and becoming resilient adults, going

74
beyond the perspectives offered by conventional Judeo-Christian beliefs while still
acknowledging and considering such ideas.
Gender is not an exclusionary factor in this research. The goal of this is to raise
awareness of the impact that adverse childhood experiences have on individuals throughout
adulthood and to explore further avenues for identifying potential gender gaps in resilience
experiences and understanding (Creswell & Poth, 2018). Furthermore, given contemporary
conceptions of gender, it is not wise to divide participants into the two genders that have
historically been practiced, as some people who would make suitable candidates might not match
these conventional gender roles. Racial and ethnic backgrounds were not a consideration for
screening and inclusion. There was a variety of backgrounds and racial or cultural sources. This
was addressed in the analysis of the data to provide information on the impact of these different
backgrounds on the outcome and results of the data received (Creswell & Poth, 2018). Differing
viewpoints were welcomed, and a multicultural sample population would benefit from the
accuracy of the data obtained (Creswell & Poth, 2018). Participants were required to have access
to the right equipment for a video-based interview. Equipment required for this includes a device
capable of streaming high-definition video and audio, as well as a reliable and consistent internet
connection. In addition, intervieweesOwere required to participate in an undisturbed, quiet place
without interruptions (Creswell & Poth, 2018).
Procedures
The study was conducted by following a set of procedures, which involve receiving
approval from the Institutional Review Board (IRB), publishing an invitation on several social
media groups to attract volunteers, screening interested individuals, and selecting a sample of
participants. Prior to sending in the invitational post, the interview questions were tested with

75
volunteers to make sure they are clear and that the interview flows smoothly. I engaged in the
process of selecting and conducting interviews with a total of 8 individuals. The selection of this
number was based on the recommended range of participants in qualitative research, which
typically falls between 5 and 25 individuals. The specific number chosen depends on the topic of
interest and the goal of achieving data saturation (Merriam & Tisdell, 2016). According to
Merriam and Tisdell (2016), data saturation occurs when recurring themes emerge in the
participant narratives. In phenomenological research, a minimum of 5Oparticipants is
recommended for data saturation (Creswell & Poth, 2018). I selected a target of 8 in order to
guarantee saturation. Data was thoroughly examined when I completed all the interviews to
verify that data saturation was attained.
Participants were able to get in touch with me directly using the contact information
provided in the invitational post. I contacted each participant andOconfirmed that every person
involved in the study has met the self-screening requirements and scheduledOan interview. The
consent form was emailed to interested participants prior to the interview for their review. The
consent form was discussed verbally, and any questions were raised with each participant during
the interview. Each participant was allocated a time slot of 60-90Ominutes for their interview.
The interviews were conducted and transcribed on Zoom. In addition, I took notes during the
interview to assist the data processing. After the interview, I asked each participant how the
interview impacted them,Oand I provided educational resources.
The Researcher's Role
My role as a researcher involved designing the interview questions, asking participants
the questions, and analyzing the data. Using relevant scholarly sources and a theoretical
framework, I created open-ended questions for the interviews in order to obtain a comprehensive

76
understanding of participants' experiences. I conducted interviews using Zoom, with the purpose
of collecting data on participants' experiences. During interviews, I utilizedOactive listening to
attentively focus on participants' verbal responses and non-verbal cues. This included observing
instances when a participant pauses and requires additional time to respond or when strong
emotions were expressed. In addition, I was able to convert the organization of all transcript data
by inputting it into the MaxQDA software application. I then compared the transcripts with the
audio recordings to verify that they were accurate.
Participants shared their experiences throughOopen-ended questions, which provided
participants with the ability to freely express their individual views and experiences without
preconceived responses (Merriam & Tisdell, 2016). Despite attempts to mitigate it, all studies
have some degree of bias (Patton, 2015). An objective, reflexive, and neutral approach is the
goal of a qualitative researcher in order to lessen prejudice (Patton, 2015). Additionally, Patton
(2015) stated that it is important for researchers to actively engage with participants rather than
remain detached. He argued that in qualitative research, it is necessary to have empathy and
engage in introspection in order to fully comprehend a person's thoughts, actions, and feelings.
During the study process, I actively strived to be self-aware of the factors that have influenced
my personal perspective of resilience. This helped me to strengthen my reflexivity and minimize
the possibility of being misguided by my own experiences or perceptions. One strategy that
helped me reduce the impact of subjective interpretation on study results was reflective
journaling, which is discussed in more depth below. The qualitative researcher actively engages
in intellectual work and deeply immerses themselves in the data, acting as the primary
instrument of study (Patton, 2015). Researchers need to be open-minded and careful in order to
avoid creating their own interpretations and preserve correct documentation (Patton, 2015). This

77
can be achieved by cross-referencing and comparing the data with the documentation (Patton,
2015).
I used reflective journaling throughout the interview process to build awareness and
distinguish my own interpretations from those of the research participants. This process involved
using memos and taking notes on my personal experiences and viewpoints. Ravitch and Carl
(2016) share that openly disclosing potential biases helps achieve validity in qualitative research.
To clearly differentiate my thoughts from the participants' responses, I set up a dedicated section
in the data analysis program to record all memos, pre- and post-interview notes, and other
personal insights. After each interview, I documented my personal reflections and emotions to
enhance self-awareness and separate my perspectives from those of the interviewees. Following
the recommendation of Patton (2015), I maintained a detailed record of every step in the research
process to ensure integrity. This audit trail allows for transparency and replicability of the study.
Additionally, I employed member checking, a technique where participants are asked to review
the findings to ensure their responses were accurately captured and conveyed the intended
message (Patton, 2015). This step adds another layer of validity to the research by allowing
participants to confirm or clarify their contributions. By implementing these reflective and
verification practices, I aimed to enhance the rigor and trustworthiness of the study while
maintaining a clear distinction between my own perspectives and those of the research
participants.
After completing the analysis of each interview, I contacted theOparticipants through their
preferred communication method and shared the translated findings from their interview. This
offered each participant a chance to verify or dispute the veracity of the findings. During member
checking, I recorded each participant's response, including whether they confirmed the answer

78
was accurate or if they pointed out an issue. After all participants emailedOme with corrections or
additional information. I followed the above procedures outlined above to lessen the impact of
prejudice and provide reliable research.
Data Collection
Qualitative researchers perceive interviews as opportunities to construct knowledge
through the dynamic exchange between the interviewer and the interviewee (Moustakas, 1994).
Phenomenological researchers predominantly rely on interviews as their principal method of data
collection (Moustakas, 1994). The qualitative researcher asks the participant open-ended
questions during the interview; the participant responds by drawing upon his or her personal
experiences. To get insight into the experiences of individuals who have successfully dealt with
childhood trauma, the researcher conducted interviews utilizing open-ended, broad questions that
specifically focused on this phenomenon. This approach was chosen as the most effective
method for gathering data (Creswell & Poth, 2018). During a 2-week period, participants were
individually interviewed on Zoom for data-gathering purposes. The interviews were recorded
using Zoom and converted into written forms through transcription. The interview offered
valuable understanding of every research question addressed in the study. Participants reflected
on their own journeys of resilience in the face of adversity, describedOthe specifics of the
traumatic event(s) they endured as children, and identifiedOany factors that have contributed to
their eventual breakthrough. Participants had the option to decline answering any question(s)
they deemed excessively distressing. All participants answered each question without deeming it
excessively distressing. In addition, participants were requested to confirm the accuracy of the
interview transcription by participating in a process called member checking (Creswell & Poth,
2018).

79
Interviews
Qualitative researchers view an interview as a process where knowledge is created
through an interaction between an interviewer and the interviewee (Creswell & Poth, 2018). The
interview is the main method of data collection for phenomenological researchers (Moustakas,
1994). During an interview, the qualitative researcher poses open-ended questions to the
participant, who responds by drawing from their personal experiences. In order to get insight into
the experiences of individuals who have successfully overcomeOadverse childhood experiences,
the most effective method for data collection was found to be conducting interviews utilizing
open-ended, broad questions that specifically addressed this topic (Moustakas, 1994). During a
2-week data-collecting period, participants were individually interviewed on Zoom. Sound
recording and transcription were utilized for each interview. The interview provided valuable
information regarding every research question addressed in the study.OThe participants were
asked to describe their experiences as people who overcame adverse childhood experiences
(ACEs), describe the type and intensity of the ACEs they had, and identify any elements of their
experiences that may have contributed to their ability to succeed in the face of adversity. In
addition, participants were requested to check the interview transcription for accuracy as part of
the member checking process (Creswell & Poth, 2018).
List of open-ended questions:
1. What does resilience mean to you?
2. In your experience of resilience, what parts of your personality or sense of self have been
most important?
3. What external factors have had the most significant impact on your resilience?
4. How do you cope with stress?

80
5. Why did you persevere in the face of hardship when you had every reason to give up?
6. What goals did you have that enabled you to endure hardship?
7. When did you make the decision to shift your focus and refuse to live as a victim?O
8. What resources did you use as a child to deal with or overcome the challenges you faced?
What factors contributed to the availability and accessibility of these resources?
9. What resources have you utilized as an adult to manage or overcome the challenges you
faced? What factors contributed to the availability and accessibility of these resources?
10. What resources do you wish you had available to help you?
11. Can you explain the psychology and emotional impact of your adverse childhood
experiences?
12. In what ways might the ACEs you went through still affect you? in your relationships,
emotionally, mentally, physically, sexually, etc.
13. What enabled you to overcome those challenges?
14. How did your relationship with Christ play a role in your transformation?
15. How did you manage to overcome these challenges?
16. Do you have any further information you would like to include?
17. Can I contact you if I have any more questions or need clarification?
The primary objective of the initial two questions was to provide a sense of comfort in
the participant, enabling them to discern what information they were willing to disclose.
According to Creswell and Poth (2018), questions asked at the beginning of the interview should
invite the interviewee to open up and talk. The purpose of questions three through seven was to
encourage reflective thinking about the participant's traumaticOchildhood experiences and the
detrimental effects those experiences had on their development from a young age. The

81
aforementioned questions initiated the interviewee's journey towards the phenomenon and
confirmed the presence of negative childhood events. The questions prompted the interviewees
to share narratives of personal encounters, relate memories, and provide reflections and
viewpoints (Creswell & Poth, 2018).
Questions eight through sixteen were designed to prompt the interviewee to think back on
the turning moment in their life, identify the elements that helped them overcome their ACE(s),
analyze the difficulties they encountered, and identify what changed the most for them. A sense
of independence, supportive family relationships, and outside resources are the three pillars of
resilience theory that help people recover from traumatic experiences in childhood (Garmezy &
Rutter, 1983). Furthermore, the purpose of these open-ended questions was to encourage "rich
talk," which allowed participants to share in-depth accounts of how they overcame hardships in
their early lives (Creswell & Poth, 2018). At the end of the interview, question 17 provided the
participant with a chance to enhance their narrative by adding more specific information
(Creswell & Poth, 2018). Question 18 provided an opportunity for the researcher to reach out
again in order to seek further clarification on the topics discussed during the interview.
Data Analysis
The researcher immerses themselves in qualitative data as part of a methodical process
known as qualitative data analysis (Patton, 2015). Data analysis is the methodical process of
reducing the volume of information generated by data collection (Patton, 2015). After each
interview, I utilized Zoom to convert the audio recordings into written form. I familiarized
myself with the data, checked for errors, and made corrections by listening to the audio
recordings while I reviewed the transcriptions. Transcription review offers several advantages,

82
such as enhanced dependability through cross-checking, proximity to the data as a researcher,
and the capacity to discern tone of voice (Patton, 20175).
Next,OI uploaded transcripts into the MAXQDA qualitative data software for the purpose
of viewing. Additionally, I organized the raw data obtained from interviews using deductive
coding techniques. I processed the data sequentially, analyzing each line and identifying words
or phrases that convey the essence of the raw data. Next, I allocated codes to pre-established
categories derived from literature, as well as theoretical notions derived from resilience theory.
As an illustration, I utilized literary and theoretical principles to categorize codes into several
groups, such as the impact of ACEs and internal protective factors associated with an individual's
microsystem.
The objective of this qualitative research was to identify significant themes associated
with the resilience phenomena and gain a comprehensive understanding of the experiences of
each participant. Hence, conducting a comprehensive examination of the exact wording enabled
me to discern patterns and themes derived from the experiences of the participants. In order to
assess the relevance of the data, I considered how it relates to the research topic (Patton, 2015).
Qualitative researchers should focus on the topic's fundamentals when drawing conclusions
(Patton, 2015). Hence, my main objective was to identify recurring patterns and themes
pertaining to the experiences of participants in relation to ACEs and resilience, which provided
insights into addressing the study issues.
After completing the thematic analysis of each interview, I synthesized the concepts
expressed by each individual participant for the purpose of member checking. In order to assist
participants in remembering and going over the primary themes of their responses, I categorized
themes using the interview questions as headers. I sent the participants an email containing the

83
identified themes from their interview. I asked them to respond via email, indicating whether
they believe the conclusions are accurate or if the themes are incorrect, along with any necessary
clarifications. This process was explained in the online consent form and during the interview,
following the interview protocol. During the ongoing interviews, I analyzed the new data and
compared it with the themes that have already been identified. This analysis helped me identify
any new themes or repeat patterns that emerged from the participants' experiences. Next, I
conducted a thematic analysis to understand the data and provide a response to the research
question.
When a component of the data complicates or poses a challenge to the comprehension
and interpretation of the data as a whole, a researcher may discover discrepant examples during
analysis (Ravitch & Carl, 2016). When inconsistencies arise, the researcher should consider
other possible causes (RavitchO&OCarl,O2016). I utilized qualitative data tools to implement the
systematic analysis process mentioned in order to identify themes within the data. The utilization
of data tools facilitated the arrangement of the narrative replies, encoding of data, classification,
documentation of emerging themes, reflective comparison of interviews, and reflective
journaling of the researcher's personal biases. Ultimately, I provided a concluding analysis of the
themes I have identified in order to address the research question and sub-questions. This was
done by utilizing specific instances from the data to substantiate the interpretation..
Trustworthiness
Findings must be credible, reliable, confirmable, and transferable in order for qualitative
studies to be considered trustworthy (Lincoln et al., 1985). Below are the methods that were used
to establish trustworthiness for this study.

84
Credibility
Credibility is determined by how accurate the data is that is provided. It guarantees that
the information supplied by the participants is appropriately reflected in the data that is
evaluated. In order to establish the credibility of this study, I incorporated direct quotations
whenever feasible and utilized member checks to validate data in cases where quotations areOnot
feasible. During member checking, I recorded each participant's response, including whether
they confirmed the answer was accurate or if they pointed out an issue. After participants
emailed me with corrections or additional information, I recordedOtheir comments and updated
the relevant interview transcript. The data and themes were double-checked through an external
audit to make sure they are credible. Additionally, the external audit provided assistance in
addressing personal biases to prevent my personal experiences from influencing the data in
support of my personal beliefs (Creswell & Poth, 2018).
Dependability and Confirmability
Dependability is the reader's capacity to have confidence in the researcher's data and
findings. Confirmability refers to the capacity of an individual to verify the data without the use
of external sources or subsequent replication of the study (Creswell & Poth, 2018). To
accomplish this, IOvalidated data by conducting member checks with participants. When
transcribing any audio and video interviews, I used transcription software and double-check the
results for accuracy. Future researchers will be able to replicate the study with greater
dependability and confirmability because of the comprehensive description of the methodologies
used in the study. The analysis was thoroughly identified and described all selected themes,
providing a comprehensive explanation of the reasons for their selection and guidance on
replicating these themes in the future.

85
Transferability
According to Miles et al. (2020), transferability is the notion that the research's findings
can be applied in different situations or circumstances. Miles et al. (2020) also discuss the
challenge of transferability in qualitative research, as it involves capturing the experiences of
actual individuals, and the practicality of fully transferring this knowledge from one context to
another may not be entirely feasible. Nevertheless, the objective was to deliver the content in a
manner that is compelling to the reader and allows them to understand its significance and
emotional connection. In order to do this, I gave thorough explanations of every aspect of the
sample population, the themes found, and the methods applied.
Ethical Considerations
Confidentiality of participant identity is a crucial component for the study. According to
Miles et al. (2020), individuals who have experienced childhood trauma frequently exhibit
feelings of shame and denial in relation to their abuse and neglect. Due to the sensitive nature of
the material collected, this study adhered closely to ethical norms and principles. Participants
were interviewed in environments that provide comfort and security, and false identities were
employed in the text to safeguard personal privacy. The presented approach takes ethical
considerations into account. The researcherOreceived approval from the Institutional Review
Board (IRB) (Creswell & Poth, 2018). The researcher did not have control over the power
dynamics between the individuals and situations (Creswell & Poth, 2018). The utmost regard
was given to ethnic and cultural distinctions at all times (Creswell & Poth, 2018). Participants
were given an explanation of the study's methods, the selection criteria, and their legal rights.
Participants provided written agreement to participate, and they were informed that their
involvement is optional and that they have the option to withdraw at any point (Creswell & Poth,

86
2018). If participants experienced discomfort throughout the data collecting process, they were
able to access a 24-hour hotline that offers professional support. Every participant engaged in the
same process of collecting-data. Each participant received a written explanation regarding the
purpose of recording the interviews, and all participants were requested to provide written
consent for these recordings (Creswell & Poth, 2018). Furthermore, all participants received
copies of their interview transcriptions for the purpose of member checking. The data was
transcribed and is being kept in password-protected digital files on the hard drive of the
researcher’s computer. These files will be securely preserved for a period of three years after the
study is finished (Creswell & Poth, 2018). During the process of data analysis and reporting, it is
essential for the researcher to honestly present all views, including data that may contradict other
conclusions (Creswell & Poth, 2018). Pseudonyms and composite reporting were used to protect
participant confidentiality throughout all data analysis, reporting, and publication (Creswell &
Poth, 2018).
Summary
The purpose of this qualitative study was to explore the lived experiences of individuals
who have successfully overcome Adverse Childhood Experiences (ACEs) and demonstrated
resilience in adulthood. The study participants are required to have a background of ACEs and
have experienced resilience in adulthood. After Institutional Review Board approval was given,
recruiting 8 study participants was accomplished through contacts on Facebook. Semi-structured
interviews were conducted through Zoom, transcribed, and analyzed for themes. The data
gathered from this qualitative study showed how participants were supported and resilient
through a variety of coping mechanisms and networks of allies, enabling them to enjoy
reasonably healthy and productive lives and normalizing conduct within their families and

87
communities. According to Becker-Blease and Freyd (2005), understanding how individuals who
experienced childhood trauma can recover is still in its early stages. Becker-Blease expresses the
optimism that in the future, we will get a comprehensive understanding of the sociocultural and
neurological transformations that contribute to this healing process.
The research questions, setting, and participant selection criteria were presented in this
chapter along with how they supported high-quality research outcomes and the study's
objectives. The study's data collection, and analysis methodologies were disclosed to ensure that
the study may be replicated in the future and to offer evidence supporting its validity. The
establishment of credibility was achieved by means of triangulation and extended interaction
with the data. Feedback from participants regarding the themes and meanings that have been
developed and were used to establish dependability. Confirmability was demonstrated through an
audit trace. The researcher's biases and belief systems were disclosed to demonstrate reflexivity.
Ultimately, the study's transferability was demonstrated by the comprehensive description of the
research procedures. Computers that are exclusively accessible to the researcher, pseudonyms to
maintain confidentiality, and the prevention and resolution of emotional distress for the
participants ensure that professional ethical standards are respected. The research conducted will
contribute to the expanding body of knowledge that will enhance theOknowledge of this subject
matter. Additionally, this study may facilitate methods of treatment for individuals who have
experienced childhood trauma.
The subsequent chapter presents the analysis of the data from this hermeneutical
phenomenological study of the lived experiences of specific individuals who have overcome
ACEs despite having suffered chronic childhood trauma. A detailed account of each participant

88
will be provided before the results of the study are discussed. Lastly, the study's topics as well as
the answers to the predetermined research questions will be discussed.

89
Chapter Four: Findings
Overview
This qualitative study investigated the lived experiences of adults who have overcome
childhood trauma and demonstrated resilience in adulthood. The research focused specifically on
individuals who reported experiencing several Adverse Childhood Experiences (ACEs) and
showed significant degrees of resilience later in life. The study employed qualitative interviews
to examine the correlation between ACEs and resilience among individuals in the Pacific
Northwest. These interviews explored ecological system-level resources that participants
identified as either advantages or obstacles for addressing ACEs and developing resilience. The
research involved eight participants, with narrative portraits based on interview data providing
extensive descriptions of each individual. The collected interview data was carefully reviewed
and analyzed to generate the reported findings. To enhance understanding of the study
phenomena, participant quotes were used to provide insight into real-life experiences of
resilience following childhood trauma. This study contributes to the understanding of resilience
development in individuals who experienced childhood trauma. By examining lived experiences
and identifying factors that contribute to resilience, the research provides valuable insights for
supporting trauma survivors and fostering resilience. The chapter concludes with a concise
summary of the themes identified during the analysis, synthesizing the key findings from the
qualitative interviews and data analysis. This research offers important perspectives on the
complex interplay between childhood trauma and adult resilience, potentially informing future
interventions and support strategies for individuals with ACEs.

90
Participants
Participants were solicited through social media platforms. An official recruitment
announcement was published, and those who expressed interest in participating contacted the
researcher, who conducted a screening to verify that they satisfied the eligibility requirements.
Before the interview, each participant received an email with the interview questions and
aOconsent form. Prior to the interview, participants gave verbal consent to participate in the
interview and have their answers recorded after going over the consent form with the researcher.
In order to safeguard their privacy, each participant was designated a pseudonym. The
participants of this study included 3 females and 3 males who reported adverse childhood
experiences. Participants were asked to provide their gender, racial/ethnic background, and age.
The participants were a multi-cultural group: 3 reported to be African American, 1 Italian, and 2
Caucasian. All participants were over the age of 26 years old. All participants identified as
having experienced adverse childhood experiences. All participants took an online ACE
questionnaire and an online resilience survey. Adverse childhood experiences (ACEs) caused by
the behavior or inaction of a caregiver or other significant adult in a child's life are the focus of
this research. While some participants sought help from therapists, others remained steadfast in
their faith in Christ alone. All participants consented to share their experiences regarding people
who have inflicted harm upon them, as well as their definition of resilience in connection with
their healing journey.
All of the study participants fulfilled the inclusion and screening requirements outlined in
Chapter Three. A word-for-word transcription of the interviews was completed.OQuotes were
occasionally utilized to provide participants with a direct chance to discuss the phenomenon.
Every participant was allocated a pseudonym to safeguard their confidentiality. A narrative

91
synopsis of the data each participant supplied during the interview is listed alphabetically below.
These provide insight into the experiences recounted by each participant and their connection to
the phenomenon.
Table 1
Participant Demographics
Name Age Gender Race
Alex 51 Male White/Black
Tachinna 38 Female Black/Puerto Rican
Vicki 58 Female Black
Mike 61 Male Italian
Patsy 70 Female Caucasian
Mikeila 61 Female Caucasian
Dale 57 Male Caucasian
Camille 59 Female Caucasian
Tachianna
Tachianna is a 38-year-old African American and Puerto Rican mother of 3 from the
Pacific Northwest. Tachianna's story is a powerful account of childhood trauma, abuse, and
resilience. Her journey begins in the foster care system and continues through adoption, severe
physical and sexual abuse, and her struggles into early adulthood. Tachianna's earliest memories
are marked by instability and trauma. She recalls "crying in a crib around age 2 and moving
through various foster homes" with her biological brother. Even at this young age, she
experienced separation anxiety when apart from her brother, highlighting the importance of their
bond amidst the chaos. Around age 4, Tachianna was adopted by a Caucasian family. While this
could have been a positive turning point, it instead ushered in a new chapter of abuse. She faced
a cultural disconnect in her new family and suffered severe physical abuse, including "being hit
with wooden spoons and metal fly swatters" and being "forced to run laps barefoot in the desert
as punishment." She was also "denied food and locked outside for extended periods." This abuse

92
created a foundation of fear, pain, and instability during her formative years. The trauma
escalated when Tachianna began experiencing sexual abuse around age 6, perpetrated by older
siblings. This abuse continued for years, profoundly impacting her self-esteem, body image, and
understanding of relationships. She was also "exposed to pornography at a young age," further
distorting her perception of sexuality and intimacy. As Tachianna entered adolescence, she
developed coping mechanisms to deal with her trauma, though some were maladaptive. She
became sexually active as a teenager, viewing it as taking back control. She also developed
aggressive behaviors as a defense mechanism. These responses, while understandable in the
context of her experiences, created new challenges for her to overcome. Tachianna's journey into
early adulthood was marked by continued struggles. She "had a baby at 18-19 years old" and
found herself in an abusive relationship with her child's father. This cycle of abuse continued
from her childhood experiences. However, she also began learning about domestic
responsibilities from her partner's mother, showing her resilience and desire to create a better life
despite the challenges.
Resilience to tachianna means to be closely tied to survival and perseverance in the face
of severe childhood trauma and adversity. Despite experiencing horrific sexual and physical
abuse starting from a very young age, Tachianna survived and made it to adulthood. Simply
enduring such trauma demonstrates a level of resilience. Tachianna shows resilience in her
attempts to avoid her abusive mother and later leave an abusive relationship with her child's
father. This suggests resilience in terms of trying to break cycles of abuse, even if she faced
continued struggles. Tachianna shared, “I left home before turning 18... Had a baby at 18-19
years old... Experienced an abusive relationship with her child's father.” Despite the negative
consequences, Tachianna demonstrated resilience in speaking up about the abuse when she was

93
younger. She stated, “ratted him out when I was... I don't know, 8 or 9.” Despite her traumatic
past, Tachianna showed resilience in trying to move forward with her life, having a child and
learning about domestic responsibilities. She notes, “I learned about domestic responsibilities
from her partner's mother.” While not always healthy, Tachianna developed ways to cope with
her trauma, showing a form of resilience. She stated, "I became sexually active as a teenager,
viewing it as taking back control. Developed aggressive behavior as a defense mechanism and
turned to alcohol as a coping mechanism.”
According to Tachianna, “resilience is the capacity to endure and persevere in the face of
overwhelming hardship.” Resilience encompasses survival, attempts to break cycles of abuse,
speaking up, moving forward with life, and finding ways (even if not always healthy) to cope
with severe trauma. She describes healing as “a complex, multi-faceted journey that involves
both internal work and external support and continues throughout one's life. She emphasizes that
while memories may remain, the emotional pain associated with trauma can diminish over time
with proper healing.” Tachianna exhibits a remarkable ability to persevere and adjust to
horrifying situations throughout her narrative, ranging from foster care to extreme assault. Her
tenacity, flexibility, and creativity are important facets of her personality that have strengthened
her resilience. When she was refused meals, she learned to survive by searching for food and
making games to deal with her situation. One of the external elements that had a big influence on
Tachianna's perseverance was her relationship with her brother, which gave her stability and
inspired her to persevere. Her development was also influenced by interactions with positive role
models, such as the mother of her ex-boyfriend, who educated her about being a woman.
Tachianna used a variety of healthy and unhealthy coping mechanisms to deal with stress.
As a child, she entertained herself and dealt with challenging circumstances by using her

94
imagination and creativity. She developed combative behavior and alcoholism as coping
strategies as she grew older. Tachianna's natural survival instinct and her desire to protect her
younger self and, later, her child were major factors in her perseverance in the face of adversity.
Her narrative reveals a strong will to overcome her situation. Finding a sense of belonging,
surviving, and eventually defending her child were Tachianna's main objectives. She was able to
persevere through her struggles because of her objectives. Tachianna said, "I stopped living as a
victim. I had a gradual process of taking control of my life, from standing up to my abusers to
leaving harmful situations."
Tachianna desired resources like reliable authority figures, ongoing mental health
support, and a nurturing, stable home environment. Throughout her childhood, she was
persistently deprived of these fundamental needs. The psychological and emotional effects of
Tachianna's adverse childhood experiences were significant. She expressed, "I developed low
self-esteem, trust issues, and difficulty forming healthy attachments." For safety reasons, her
experiences made her angry and gave her a combative attitude. Tachianna overcame her
obstacles by relying on her inner strength, faith in God, learning from mentors, and making
tough choices to leave dangerous situations. As she works through and recovers from her terrible
experiences, it seems that she will continue to overcome these obstacles.
Vikki
VikkiOis a 58-year-old African American woman residing in the Pacific Northwest. She
has been married for 40 years and has 3 children. According to Vikki, the ministers at her church
and her adoptive parents were significant individuals in her early life. “As a child, I was greatly
influenced by the good religious leaders we were constantly surrounded by.” Vikki stated that
her adoptive father has died and that she still maintains contact with her adoptive mother. She

95
does not have contact with her biological parents. Before being adopted at the age of seven,
Vikki said she had experienced trauma while living with her birth parents and in foster care. "My
parents were involved in drug use." My father was incarcerated. Thus, writing letters constituted
a significant portion of our connection. She was encouraged to correspond with her biological
father while he was incarcerated, even after she was adopted. She said her father had promised
her a number of things regarding his intentions toward her. As usual, these promises were
broken. As a result, I had a bad experience with having high expectations for so long as a child.
and the fact that I still wasn't selected. Vikki added that she was abused by her adoptive father as
a child, but she did not realize it was wrong for a long time.
Vikki shared, “there was abuse in the home, including physical, mental, and emotional
abuse. Although I was aware of it, I was unaware that it was abuse. I believed that this was the
standard because I was adopted, as they had biological children. It is true that they are regarded
with less respect simply because they are not considered to be genuine children.” Because of her
adoption, Vikki believed it was natural to be treated differently. No one in the house gave her the
benefit of the doubt; they all pretended everything was fine. Since she received her education at
home, she did not have many opportunities to hear other points of view. Due to her early
marriage and husband's position as breadwinner, Vikki feels a great deal of sympathy for her
adopted mother. No matter what my dad said, she would always agree. Vikki shared that due to
the fact that she was raised in the manner in which one is expected to be a wife, she became a
minister's wife and became the helpmate. The lessons she had learned made it easy for her to
witness neglect and abuse but prevented her from doing anything about it. When Vikki's
adoptive father died, her mother expressed regret to her for letting him mistreat her. According to
Vikki, she has more complex feelings for her biological parents. Vikki stated, "I've come to

96
terms with the fact that my father will never pick me over his drug use. She claimed that
although she has partially forgiven him, she is still upset by his actions because they are still
painful. According to Vikki, her mother never showed any signs of wanting a relationship. She
consistently stated that she had no desire to become a mother. Vikki stated that it is effortless to
exhibit forgiveness toward her, as she "never attempted to disguise herself as anything other than
her true self." According to Vikki, there was a time when she tried to change her mother and
have a different connection with her.
Vikki feels a sense of understanding towards her mother for her candidness about not
desiring the role of a parent. In the face of these challenges, Vikki exhibited remarkable
resilience by enduring early trauma and instability within her birth family and during her time in
foster care. Persevering through and ultimately acknowledging the mistreatment in her adoptive
environment. Enduring her marriage for 40 years while facing neglect and abuse, confronting the
realities of her biological father's addiction and decisions, and coming to terms with her
biological mother's lack of interest in parentingOwhile admitting her continued hurt, she is
partially forgiving of her biological father. Vikki's narrative illustrates her journey of self-
forgiveness towards her biological mother, highlighting her resilience in the face of numerous
challenging childhood experiences and complex family relationships. She has steadily
progressed towards understanding, acceptance, and ultimately, forgiveness. Her resilience is
clearly demonstrated through her long-term marriage, the upbringing of her children, and her
capacity to navigate her intricate family history. Vikki hoped for healthier relationships,
counseling, long-term support, and increased education about the effects of emotional, physical,
and psychological abuse.

97
Mike
Mike is a 61-year-old male of Italian descent residing in the Pacific Northwest. He was
raised in a challenging home environment. He outlines the backgrounds of his parents: "My mom
struggled with alcoholism, and my dad dealt with military PTSD." During the Korean War, he
served as a corpsman, positioned near the front lines, which resulted in him experiencing
significant PTSD. He shared,O"my mom and dad wereOabusive." It seems unlikely that my
parentsOacted with intentional neglect. Mike recounts his experience of being molested as a child:
"I was molested when I was a kid by a babysitter." His family life deteriorated further: "My dad
left when I was 12, and my mom moved out of the house when I was 15." During his teenage
years, Mike faced challenges with substance use: "I was involved in a lot of drug use and things
like that." Mike shared, "by the time I left, I had missed 27 days in one quarter and was using
drugs."
Mike's life changed after a spiritual experience: "After I met Jesus. You know I wanted to
finish my schooling, so I sort of dropped back in." He eventually completed his high school
education. Regarding his recovery and resilience, Mike shared, “I think resilience is a reflection
of the therapy of healing that God takes you through to restore and bring well-being where you're
not. Well, you're not well in relationships. You can't trust people you can't communicate with.”
He describes his personal growth: “I wouldn't call myself an introvert anymore. That was a part
of my trauma" and "my favorite part is that I can connect with people now where I couldn't. I can
love people now, and before I was utterly broken.”
Throughout his journey, Mike highlights the importance of understanding trauma as an
injury that requires healing, rather than a personal flaw. He credits his faith and the healing
process for his transformation and increased ability to form meaningful connections with others.

98
Mike's story illustrates how resilience can involve profound personal transformation, addressing
deep-seated trauma, and developing new capacities for connection and love. His experience
highlights the role of faith in the healing process and the potential for growth even after
significant adversity.
Patsy
Patsy is a 70-year-old Caucasian woman from the Pacific Northwest. She lived in a 2-
parent household with severe ongoing sexual abuse. Her mom tried to protect her from the abuse
from her father, but her mother could not divorce her father due to her being illiterate and unable
to work. Patsy experienced sexual abuse as a child, which she alluded to when describing a
confrontation with her abuser: "he hadn't bothered me for a while. but nobody was home, and he
came upstairs. There was no reason for him to be up there." She struggled with suicidal thoughts,
saying, "I went through wishing that I'd never been born, wishing that I was dead, and then
thinking about ways that I could commit suicide."
Patsy found resilience through self-reliance and pride. She stated, “self-reliance. my
pride, which is a negative as well as a positive knowing that I did not deserve what was
happening to me.” At 14, Patsy took a stand against her abuser: “I told him that if he didn't leave,
I was going to tell. and he never bothered me after that.” At 18, Patsy had a revelation: “I'm 18.
I'm on my own. Whatever happened before is on my parents. What I do from now on is up to
me.” Patsy developed various ways to cope with stress, including crying, faith, and journaling:
“Now, if I'm having my very best day, I take it to Jesus 1st thing... I journaled I talked to my
husband or my accountability partner.” Despite her hardships, Patsy maintained goals that helped
her endure: "I wanted to go to college. I wanted to be a teacher or a social worker. and I wanted
to get married and have a good family.” Patsy also mentioned that sometimes she realizes she's

99
stress eating, though this seemed to be more of an observation than an intentional coping
strategy. She emphasized that while she tries to turn to her faith immediately when stressed, she
doesn't always do so right away: “eventually I do. Sometimes I don't do that immediately."”
Patsy highlights self-reliance and pride as fundamental traits of her character that played
a significant role in her resilience. She additionally notes external influences like the lessons of
responsibility, the role of school as a refuge, and the presence of friends in the community. “Self-
reliance. My pride, which is negative as well as positive. Knowing that I did not deserve what
was happening to me and that the adults in my life were not in control of their finances for sure.”
As a child, Patsy coped with stress primarily through crying. She shared, “I cried a lot. That was,
that was my release.” As an adult, she has developed various coping mechanisms: “Now, if I'm
having my very best day, I take it to Jesus 1st thing... I journal. I talked to my husband or my
accountability partner. Sometimes I realize I'm stress eating... doing my Bible study and reading
the Bible.” Patsy’s faith played a crucial role in her resilience and transformation. She mentions
taking her stress to Jesus and using Bible study as a coping mechanism. She shared, “Every once
in a while, he gives me these revelations. And it was like, okay. I'm 18. I'm on my own.
Whatever happened before is on my parents. What I do from now on is up to me.”
Overall, Patsy’s stress coping methods have evolved over time, moving from primarily
emotional release (crying) to a mix of spiritual practices, social support, and distraction
techniques. Patsy attributes much of her resilience to her faith, often mentioning Jesus and the
Holy Spirit as sources of guidance and strength. Through these experiences and coping
strategies, Patsy demonstrated remarkable resilience in overcoming her childhood trauma and
building a life focused on healing and growth.

100
Mikeila
Mikeila is a 61-year-old Caucasian woman raised in the Pacific Northwest. Her adverse
childhood experiences began even before she was born, as she explains, “The more I've learned
that mine started pratctically before I was even born, because, my mom had me induced on the
4th of July so she wouldn't have to miss too much grad school.” This early disruption set the
stage for attachment issues and a sense of abandonment. From infancy, Mikeila experienced a
lack of consistent maternal care and attachment. She shared, “I was right away put with
caregivers. At least one of them was my grandma. But like I had to be with people that weren't
my mom.” She notes that “the attachment that needed to happen didn't happen.” This early
separation from her mother had lasting effects on Mikeila's sense of self and security. Mikeila's
mother's own unresolved trauma contributed to the intergenerational transmission of trauma. She
shared, “my mom had her own dissociation and adult children issues from trauma that she had
never dealt with and never did deal with.” This led to Mikeila inheriting unresolved trauma:
“Basically, I got passed on what was done to her.” Growing up, Mikeila experienced a pervasive
sense of shame and inadequacy: "I always felt like something was missing or something just like
I wasn't good enough, or I just. I just had this feeling of shame." This shame was deeply rooted
and had long-lasting effects on her self-esteem. In addition to emotional neglect, Mikeila also
experienced physical abuse from her schizophrenic brother. She stated, “my brother was
schizophrenic and had a terrible temper... he just liked to beat me up all the time and stuff, and
no one protected me from that.” This ongoing physical abuse added another layer of trauma to
her childhood experiences. Mikeila's parents were addicts, which further complicated her home
environment. She shared, “they definitely were highly educated and added money and covered
everything up with what they're looking good.” The addiction led to violence in the home,

101
particularly from her father: "my dad would get drunk, and his violence when he was drunk, was
the worst.” These adverse childhood experiences had a profound impact on Mikeila's
development and led to destructive behaviors later in life. She shared “I was very traumatized at
a very young age and didn't even know that was going to lead me down a path of self-
destruction, of drugs and alcohol and other things that I eventually recovered from."
Despite these challenges, Mikeila demonstrated resilience by continually seeking ways to
improve her life. She states, "I just kept on never giving up.” This persistence led her to explore
various support systems and therapeutic approaches. Mikeila credits support groups and therapy
as significant factors in her healing journey: “Lot of my support groups and my therapist stuff.
It's good.” A key aspect of Mikeila's resilience has been her commitment to self-love and
understanding. She describes learning to love all parts of herself, including her “inner child that's
hurt” and her “critical parent.” This process of self-acceptance has been crucial to her healing.
She shares, “I've learned how to love them all.” Mikeila's resilience is also evident in her ability
to reflect on her experiences and recognize her growth. She acknowledges the ongoing nature of
her healing journey: “I'm still learning how to do that one,” referring to coping with stress.
However, she also notes her progress: “I am better at it, and I know I have yoga, and I know how
to... I have tools about deep breathing and just, you know, and self-talk.” In recent years, Mikeila
has found additional strength through her developing relationship with Christ. While this is a
newer aspect of her journey, she finds comfort in it: “I just feel like I have another person to talk
to that I can trust, that cares about me.” Throughout her story, Mikeila demonstrates that
resilience is not about avoiding pain or difficulty but about continually striving to heal and grow
despite adversity. Her journey from a traumatized child to a self-aware adult committed to
ongoing personal growth is a powerful example of resilience in action.

102
According to Mikeila, she had limited resources available to her as a child to cope with
her adverse experiences. She mentions that her primary resource was her grandmother, stating,
"Well, I didn't really have any resources other than Grandma Susan." This suggests that Mikeila
had at least one supportive adult figure in her life, which research shows can be a significant
protective factor for children experiencing adversity. Mikeila also participated in gymnastics,
which she describes as a distraction but not necessarily a true resource: “I did use my gymnastics
a lot to distract myself, but it didn't really do anything for me, as far as resources, though you
know what I mean, like.” This indicates that while she had some activities to occupy her time,
they did not provide the deeper support or coping mechanisms she needed to deal with her
trauma.
When asked about resources she wished she had, Mikeila initially struggled to answer,
saying, "Oh, I don't know. You know, I just can't go back and even wonder because I just those
are just blank parts of my life." This response suggests that the trauma she experienced may have
impacted her ability to fully process or remember aspects of her childhood, making it difficult for
her to identify specific resources she lacked. However, when prompted about therapy, Mikeila
acknowledged that it might have been helpful, but with a caveat: "Nice. But then again, I don't
know if it would have been any good if my parents hadn’t been in therapy." This response
indicates that Mikeila recognizes the potential value of professional mental health support but
also understands that her parents' involvement and healing would have been crucial for any
intervention to be truly effective.
Mikeila also implied that she wished her parents had been more aware and supportive,
stating, “Parents would have been more in touch with the reality of. You know they were
educators, and they thought they knew everything. But they were missing an awful lot of stuff.”

103
This suggests that she wished for more understanding, recognition, and support from her parents
regarding her experiences and needs. Overall, Mikeila's responses indicate that while she had
minimal resources as a child, she now recognizes the potential value of comprehensive family
therapy, parental awareness and support, and professional mental health interventions for
children experiencing adverse childhood experience.
Alex
Alex is a 51-year-African American and Caucasian man. He grew up in Portland with his
mother and brother. Alex's adverse childhood experiences were numerous and severe, beginning
in his early childhood and continuing through his teenage years. He grew up in northeast
Portland in a challenging environment, with a mother who was heavily involved in drugs and
partying. Alex shares, “my mom came out of the hippie era. Just really got involved quite a bit
into the drugs and sex and just partying lifestyle.” Alex lived in public housing projects as a
child, though he didn't realize the nature of his living situation at the time: “I didn't know that it
was that, you know, until someone tells you that's where you live.” Alex was exposed to a great
deal of violence in his community from an early age. He talks about a number of horrific events,
including “One of my friends' dads was killed at my doorstep.” Additionally, Alex shared,
“another friend's dad was beaten into my house with his girlfriend.” He also experienced sexual
abuse starting around age 6. He describes two separate incidents as: “I was molested as a child
by a woman. It was a neighbor, a gal who was babysitting us.” Alex also shared, “Eric took me
into a field one time, and he made me suck his his penis.”
Furthermore, Alex was exposed to ongoing gang activity in his neighborhood. “Gangs
were coming in the Crips and the Bloods at that time it was the early eighties or late seventies.”
Alex also struggled in school and had traumatic experiences there as well: “When I was in 3rd

104
grade, a teacher decided that she was going to make me sit under her desk and one time she tied
me to my chair with a jump rope.” Overall, Alex's childhood was marked by instability, violence,
abuse, and exposure to drugs and crime from a very young age. These experiences had profound
impacts on his development and life trajectory.
Alex's story of resilience is a powerful testament to overcoming severe childhood trauma
and adversity. His journey illustrates both the long-lasting impacts of abuse and the human
capacity for healing and growth. From a young age, Alex faced numerous challenges, including
poverty, exposure to violence, and sexual abuse. Despite this environment, Alex initially found
ways to cope and even enjoy aspects of his childhood. He shared, “there was lots of fun at
Carlton Court, too. We played on the swing. We played on the swings, we rode bikes, and we
were allowed to just ride everywhere.” However, Alex also experienced sexual abuse, which had
a profound impact on him. These traumatic experiences led to feelings of shame and confusion,
which affected Alex's self-esteem and relationships for years to come.
As Alex grew older, he faced additional challenges, including struggles in school and a
complex family situation. He discovered in his teens that the man he thought was his father was
actually in prison for murder. Despite these setbacks, Alex showed resilience by continually
seeking ways to improve his life: “I started focusing on my grades. In the 7th grade, I had a goal.
I had a focus... and I got great grades because I had a purpose, and I got into Benson.” Even
when he faced setbacks, like being kicked out of Benson High School, Alex found ways to adapt
and move forward. He took on various jobs and pursued entrepreneurial opportunities: "I started
hitting sales goals, and then the process of that I had decided I'm going to go back and get my
high school diploma.” While Alex didn't complete his high school education in a traditional way,
he continued to learn and grow through his work experiences and personal development: “I was

105
learning all these books and reading all these things about Think and Grow Rich, and was going
to start going to church.”
Perhaps one of the most significant demonstrations of Alex's resilience was his response
to personal heartbreak. When faced with depression after a relationship ended, he chose to
channel his energy into self-improvement: “I went to the gym, and 6 months later I came out
completely shredded, like I had lost 55 pounds. I had gotten down into like these ripped abs,
muscles, and shoulders.” This transformation led to new opportunities and marked the beginning
of his fitness career, showing how Alex was able to turn adversity into opportunity. Alex says
that he was diagnosed with ADHD as an adult, which suggests that he did not get the right
diagnosis and help for this condition when he was a kid. He shared, “I've had trouble in school
all my life. I didn't know this before. I mean, I was told I had ADHD as an adult.” Alex shared he
would have liked to have a more positive male role model to teach him how to be a man. Alex's
relationship with his father was complicated and inconsistent. He mentioned, “I would talk to
him on the phone, maybe once every 3 months to 6 months, and he was a cook, and he cooked
for a lot of people, he was too busy to come see us.”
Based on Alex's interview, Christ played a significant role in his transformation and
healing process. While Alex doesn't explicitly describe a dramatic conversion experience, he
mentions several ways that faith and spirituality became important in his journey: Alex describes
how he began exploring spirituality and self-improvement in his young adulthood: “I was
learning all these books and reading all these things about Think and Grow Rich, and I was going
to church.” This suggests that attending church and engaging with spiritual teachings was part of
Alex's early efforts to improve his life and overcome his past trauma. When faced with

106
depression after a difficult breakup, Alex channeled his energy into physical fitness, which he
seems to connect to a spiritual transformation.
Alex also mentions developing a relationship with Christ more recently. He shared, “I
just feel like I have another person to talk to that I can trust, that cares about me.” This suggests
that Alex's faith in Christ has become a source of comfort and support in his ongoing healing
journey. Throughout the interview, Alex demonstrates a reflective and growth-oriented mindset,
often attributing positive changes in his life to spiritual or personal development work. Alex
shared “It's a healing walk, and it's both transformational. It's therapeutic; it's restorative.”
Christ's role in his transformation, it's clear that spirituality and faith have become important
components of his resilience and ongoing healing process. Alex has managed and overcome his
childhood struggles as an adult by using a variety of services. He says: "I've done a lot of work in
therapy, so I'm speaking to you calmly right now. To enjoyed my life and I've done a lot of
things.” This implies that he has processed his experiences through therapy or other personal
development activities. Alex's narrative demonstrates the emotional and psychological effects of
his traumatic early experiences. He talks about how his experiences with sexual abuse and
unstable families have left him feeling ashamed, afraid, and confused. His difficulties
concentrating and performing well in school, as well as possible trust issues in relationships,
were probably exacerbated by these events.
Alex's perseverance, adaptability, and willingness to face his history appear to be the
foundations of his capacity to overcome these obstacles. In addition to gaining an understanding
of his own actions and difficulties, he has been able to process painful events and build new
relationships, including with his father. It's evident that Alex has had substantial personal
development and healing, he discusses his relationship with Christ or his transformation. He has

107
demonstrated a level of composure and clarity in reflecting on his experiences, indicating that he
has made significant efforts to comprehend and reconcile his history. Throughout Alex’s
interview he shared a deep relationship between continual self-work, outside support, and
personal resilience in surviving extreme adverse childhood experiences. His story demonstrates
the potential for development, healing, and transformation while also highlighting the long-
lasting effects of traumatic childhood trauma.
Dale
Dale is a 57-year-old Canadian residing in the Pacific Northwest. He grew up in a
Christian home with his brothers and sisters. His parents were very active in his life and provided
a stable living environment, food, and clothing. Dale’s parents believed in opening up their home
to provide transitional housing for convicted felons. At the age of 11, Dale experienced severe
sexual abuse at the hands of a man his parents had invited to live with them. This abuse
continued for about a year and a half, escalating to involve multiple abusers and threats of
violence. Despite the trauma, Dave found strength in his faith and the support of others. He made
the crucial decision to leave home at 14, which marked a turning point. Dale stated, “when I was
14 and a half. I made the decision that I had to leave home because I had to get out of the
situation.” This decision to remove himself from the abusive environment was a key step in
Dale's journey towards healing and resilience. He found support in a new community,
particularly from a compassionate pastor. He shared, “There was a pastor there who didn't know
all of the situation but was so fatherly, you know, and compassionate to all of us.” Dale’s
resilience was rooted in his faith and his sense of purpose. He shared, “I just knew that I'd gone
through a lot of hits, and I still got back up, and I was still standing, and I was still being used by
God.” He emphasized the importance of having people around him who could relate to his

108
experiences and push him towards healing: “I needed people around me that had the experience.
I wanted people around me that believed in me as a person.” Dale's approach to coping with
stress and maintaining resilience involved staying busy and focused on productive activities.
Dale shared, “I cope with stress by staying busy. You know the busyness of things to be able to
just and feel like I have something to accomplish every day that helps me with stress.”
Ultimately, Dale's resilience was driven by his belief in a higher purpose for his life. Dale shared,
“I didn't have every reason to give up because I believed that there was something in my life that
I needed to fulfill.”
In conclusion, Dale's story illustrates how resilience can be built through a combination
of personal determination, faith, supportive relationships, and a sense of purpose. Despite
experiencing severe trauma at a young age, Dale was able to not only survive but thrive, using
his experiences to fuel his personal growth and later his ministry to others. His journey
underscores the power of resilience in overcoming even the most challenging circumstances.
Camille
Camille is a 59-year-old Caucasian woman from the Pacific Northwest. Her earliest
memory of abuse is from when she was about 5 years old, involving her father. She recounts,
“we had an outhouse, and he informed Mom that he was going to take me out to go to the
bathroom before bedtime. It was dark... I remember being so excited because I never had any
alone time with Dad... I was skipping along, holding his hand, heading out to the bathroom, so
thrilled for this just time alone with Dad.” This innocent excitement quickly turned to horror as
her father sexually abused her in the outhouse. Camille describes the confusion and fear she felt,
as well as her father's threats to keep her silent. The abuse continued for years, with Camille
actively trying to avoid her father. When she was 8 or 9, she finally told someone about the

109
abuse, but the response was devastating: “Nobody approached me. As a matter of fact, the older
siblings were angry at me that I started this big... scene, and if I hadn't opened my mouth and I
started thinking, oh, my God! I wish I hadn't said anything.” Camille also experienced sexual
abuse from her brother when she was 12.
Later in life, she discovered that her father had abused other sisters as well. Despite these
traumatic experiences, Camille demonstrated remarkable resilience. She defines resilience as
“being able to just keep your head up and keep pushing forward... even in adversity or hardship,
or whatever, just to be able to stand and stand firm.” A key part of Camille's healing process was
forgiveness. She states, “I would have still been able to say to him, I forgive you like God
forgives... and he throws it in the sea of forgetfulness... I'm not going to bring that up to you ever
again. But I'm just going to forgive you.” Camille also had to work through sexual issues in her
marriage as a result of her abuse. She explains, “I didn't really recognize that I still had some real
sexual issues until after I became a Christian... that was the thing about not being able to relax
and enjoy being with my husband.” Through her faith and personal growth, Camille was able to
overcome these challenges. She shared, “until I was able to let God heal me from and
reinterpreting what a healthy, loving, sexual relationship was all about... it wasn't until then that I
was able to actually relax and enjoy being with my husband that way.”
Camille emphasizes the importance of forgiveness, stating, “I would have still been able
to say to him, I forgive you like God forgives... and he throws it in the sea of forgetfulness.” Her
approach to dealing with her trauma also influenced how she raised her own children,
emphasizing open and honest communication about sensitive topics. This is evident in her
anecdote about explaining pregnancy to her young daughter. In conclusion, Camille's resilience
is characterized by her ability to forgive, her faith in God, and her determination to live a life not

110
defined by her past traumas. Her story highlights the complex and long-lasting effects of
childhood sexual abuse while also demonstrating the possibility of healing and growth.
Results
The data presented below resulted from participant responses collected from
semistructured interviews using the data collection methods described in chapter three. To
conduct this thematic analysis, I followed a systematic approach that involved several key steps.
First, I thoroughly familiarized myself with the interview data by reading and re-reading the
transcripts multiple times. This immersion in the data allowed me to gain a comprehensive
understanding of the participants' experiences and narratives. Next, I began the coding process. I
used an inductive approach, allowing codes to emerge from the data rather than imposing
predetermined categories. I started with line-by-line coding, carefully examining each segment
of text and assigning descriptive labels to capture the essence of the content. As I progressed, I
refined and consolidated these initial codes into more focused categories. To move from raw data
to codes to themes, I employed a constant comparative method. I continuously compared new
data with existing codes, identifying patterns and relationships. As codes began to cluster around
similar concepts, I grouped them into potential themes. I then reviewed these themes against the
entire dataset to ensure they accurately represented the participants' experiences.
This exercise yielded three main themes that emerged directly from participant responses.
The first theme, having a sense of purpose and calling, consists of four codes: mission, vocation,
life direction, and meaningful work. The second theme, receiving support from others, is based
on the participants' narratives about their healing process. This theme yielded five
codes:Omentorship,Ocommunity,Ofamily support,Oprofessional help, andOpeer relationships. The
third theme, faith in God and His transformative power, revealed four codes:Ospiritual

111
guidance,Odivine intervention,Oredemptive suffering, andOtranscendent purpose. The themes and
codes are outlined in Table 2: Theme Development.
Table 2
Theme Development
Themes Codes
Having a Sense of Purpose or Calling Mission
Vocation
Life direction
Meaningful work
Support from Others Mentorship
Community
Family support
Professional help
Peer relationships
Faith in God and His Transformative Power Spiritual guidance
Divine intervention
Redemptive suffering
Transcendent purpose
Three major themes emerged from the thematic analysis of the interviews among those
who showed resilience following childhood trauma: faith in God and His transformative power,
having a sense of purpose and calling, and receiving support from others. These themes were
consistently present across the participants' lives, highlighting their significance in the resilience
process. Within these themes, two separate clusters formed, with contrasting means of
overcoming adversity. The first group, including Dale, Mike, and Alex, showed a strong sense of
purpose from an early age closely tied to their faith. For example, David shared, "I knew I had a
call on my life," even as a teenager, which provided him with the strength to persevere through
adversity. Similarly, Mike described how his faith helped him overcome adversity and find
meaning in his struggles, contributing to his resilience. The second group included Tachianna,

112
Patsey, Mikeila, Vikki, and Camille, who developed their sense of purpose later in life as part of
their healing journey. Although it took these individuals longer to recover from trauma and find
meaning in their experiences, in the end, they developed a strong sense of purpose that
strengthened their resilience. Support from others was significant to the resiliency of both
groups. This support came from different sources, including pastors, mentors, and supportive
family members. Most participants shared how these relationships provided encouragement,
guidance, and a sense of belonging that was the center of their healing process.
Faith emerged in both groups, with many participants describing how their spiritual
beliefs provided comfort, guidance, and a framework for understanding and overcoming their
traumatic experiences. For all, faith was a source of strength throughout their lives, and it
became increasingly important as they worked through their trauma. These themes bring out the
complicated way that internal and external factors work together to make people who have been
through adverse childhood experiences. It is apparent that resilience is not a fixed trait but rather
a process that is developed by one’s faith, the presence of supportive relationships, and the
capacity to give one's events meaning and purpose.
Theme Development
Recurring themes emerged quickly from the participants' responses during the interviews.
Initially, I documented significant similarities identified throughout the interviews. During the
transcript review and cleanup, major themes developed. While I was collecting data during the
interviews, I utilized a systematic approach to evaluate the consistency of previously identified
themes among participants. During this process, I identified the emergence of three distinct
themes. The narratives of Tachianna, Vikki, Mike, Patsy, Mikeila, Dale, Camille, and Alex
revealed three similar themes that played important roles in their journeys of resilience and

113
healing: faith, support in the community, and having a sense of purpose or calling. These themes
emerged as common themes across all participants that helped these individuals navigate through
severe adverse childhood experiences, ultimately leading to personal growth and transformation.
Faith provided all participants with a framework for understanding their experiences, a source of
comfort, and a path towards forgiveness and healing. Support from the community offered
supportive connections when these individuals felt alone and vulnerable. Finally, having a sense
of purpose or calling gave participants direction and motivation, helping them to persevere
through adversity and find meaning in their lives. Together, these themes demonstrate how
individuals can utilize beliefs, external support systems, and purpose to overcome the most
challenging of circumstances and build resilient, meaningful lives.
Table 3
Coding Framework Table
Code Description Example
Purpose Expressions of having a sense
of purpose or calling
I knew I had a call on my life
Support Instances from receiving
support from others.
Mentions of encouragement
from pastors or mentors
Faith References to faith in God Descriptions of how faith
provided comfort and
guidance
Having a Sense of Purpose or Calling
A sense of purpose or calling was an important factor in developing resilience among all
interviewees. Throughout the interviews of Tachianna, Vikki, Mike, Patsy, Mikeila, and Alex,
Camille, and Dale discovered their purpose provided them with direction, motivation, and
guidance for personal growth. Purpose showed up in different ways, such as working toward

114
educational and job goals, spiritual connections, or helping others. It gave everyone involved a
purpose to keep going and a hope for a better future, acting as a beacon of hope. In addition to
assisting people in overcoming their traumatic experiences, the idea of a feeling of purpose or
calling was essential to their continued recovery and personal development.
Dale
Dale's journey of resilience and healing was deeply rooted in his purpose and calling.
Despite experiencing severe adverse childhood experiences, Dale found strength and direction
through his faith in God and belief in a higher purpose for his life. He shared, "I didn't have
every reason to give up because I believed that there was something in my life that I needed to
fulfill." This conviction gave Dale the motivation to persevere through his adversities and work
towards healing. The way he approached everyday life also demonstrated his sense of purpose;
he shared, "I cope with stress by staying busy. You know the busyness of things to be able to just
and feel like I have something to accomplish every day that helps me with stress." Dale’s focus
on productivity and accomplishment helped him maintain his resilience and continue living his
life. Furthermore, Dale's desire to cultivate relationships with others who might relate to his
struggles and encourage him to heal demonstrated that his purpose included serving others: "I
needed people around me that had the experience. I wanted people around me that believed in
me as a person." This desire to help others who had faced similar challenges suggests that Dale
found purpose not only in his own healing but also in supporting others who have gone through
similar trauma.
After surviving childhood trauma, Dale's story demonstrates his path to healing and
resilience through severalOthemes and codes, receiving support from others, a sense of purpose
and calling, and faith in God and His transformative power. Dale’s belief that "there was

115
something in my life that I needed to fulfill" demonstrates a deep-rooted purpose that provided
him with the motivation to persevere through adversity. This conviction gave Dale a reason to
keep going but also shaped his approach to daily life and personal growth. Dale's faith-driven
resilience emerges as another key element in his story. His ability to overcome challenges and
persevere was deeply rooted in his spiritual beliefs. His faith in God provided him with strength
and served as a framework for understanding his experiences, contributing significantly to his
healing process. An interesting and somewhat unexpected aspect of Dale's story is his use of
productivity as a coping mechanism.
Dale's intentionally sought out people who could relate to his experiences and believe in
his potential. This highlights the crucial role that receiving support from others plays in the
healing process. Dale's story also reveals how his sense of purpose extended beyond personal
healing to helping others on similar journeys. The unique code of "busyness as a coping
mechanism" that emerged from Dale's story offers an intriguing insight into how purpose can
serve as a tool for managing trauma-related challenges. While productivity is often associated
with purpose, Dale's specific use of productivity to cope with stress presents a different
perspective on the practical applications of having a sense of purpose in daily life. In conclusion,
Dale's experiences were shared with the broader themes identified across participants while also
revealing unique aspects of his personal journey towards resilience and healing. His story
exemplifies how a sense of purpose, faith in God, and supportive relationships can work together
to foster resilience and facilitate healing from adverse childhood experiences.
Camille
Camille's journey in finding a sense of purpose and calling is deeply rooted in her healing
process and her faith. Despite experiencing severe adverse childhood experiences, Camille found

116
strength and direction through her commitment to forgive and her faith in God. She shared, "I
would have still been able to say to him, I forgive you like God forgives... and he throws it in the
sea of forgetfulness." This act of forgiveness became the center of her healing journey and gave
her a purpose in breaking the cycle of trauma. Camille's purpose also showed up in her approach
to her marriage and personal growth. She shares, "until I was able to let God heal me from and
reinterpreted what a healthy, loving, sexual relationship was all about... it wasn't until then that I
was able to actually relax and enjoy being with my husband that way." Her transformation in her
marital relationship demonstrates how her purpose helped her create a healthier, more fulfilling
life for herself and her family. Furthermore, Camille's commitment to open and honest
communication suggests that she found purpose in breaking generational patterns of secrecy and
shame.
Several key codes emerged from Camille's narrative:
Faith-driven resilience: Camille's faith in God offered her strength and guidance during her
healing journey.
Forgiveness as healing: Forgiveness developed as a significant means for personal development
and disrupting patterns of trauma.
Breaking generational patterns: Her commitment to open communication with her children
indicates a purposeful effort to disrupt generational trauma.
These codes connect to the three major themes of having a sense of purpose and calling,
receiving support from others, and faith in God and His transformative power. Camille's
experiences illustrate the interconnectedness of these themes, promoting resilience and healing
from childhood trauma. The reinterpretation of closeness is one unusual or distinctive code that
surfaced in Camille's story. She shared, "what a healthy, loving, sexual relationship was all

117
about" offers a great perspective on how healing can transform a person’s understanding of
intimate relationships. This code highlights the significant influence that a sense of purpose and
faith may have on many aspects of life, including even the most intimate and vulnerable areas.
Patsy
Patsy's sense of purpose and calling showed up in her journey despite experiencing
severe sexual abuse. Patsy found strength and direction through her faith and personal goals. She
shared, "I wanted to go to college. I wanted to be a teacher or a social worker. and I wanted to
get married and have a good family." These goals gave her something to work for beyond her
immediate circumstances. Patsy's faith also played a crucial role in shaping her purpose. She
shares, "Now, if I'm having my very best day, I take it to Jesus 1st thing," indicating that her
faith in God provides her with guidance and strength. This purpose is further expressed when she
shares, "Every once in a while he gives me these revelations. And it was like, okay. I'm 18. I'm
on my own. Whatever happened before is on my parents. What I do from now on is up to me."
This realization was the beginning of a turning point where Patsy takes ownership of her life and
future, driven by a sense of personal responsibility and purpose. Her commitment to journaling,
Bible study, and maintaining accountability partnerships also demonstrates her dedication to
personal growth and living with a purpose.
Several key codes emerged from Patsy’s narrative:
Faith-driven resilience: Patsy's faith in God provided her with guidance and strength throughout
her healing journey.
Personal aspirations: Her clear goals for education, career, and family life gave her something
to work for an look beyond her immediate circumstances.

118
Personal growth practices: She was committed to journaling, Bible study, and accountability
partnerships.
Patsy's story reveals a strong connection to the broader themes identified in the study of
resilience among survivors of adverse childhood experiences. Her goals for college, career, and
family life directly relate to the theme of having a sense of purpose and calling. These desires
provided Patsy with a clear direction and motivation, helping her to overcome the challenges she
faced. The theme of faith in God and His transformative power is shown by how much Patsy
relies on spiritual direction and revelations. Her habit of giving her best days to Jesus first and
her experiences of divine revelations show how important her faith was in giving her a sense of
purpose and strength as she healed. Even though Patsy doesn't say it, the fact that she keeps up
accountability partnerships shows how important supportive relationships are to her journey,
which ties in with the idea of getting help from others. As she worked toward her goals and
continued to grow as a person, these partnerships probably gave her support, advice, and a sense
of belonging as she did so. These links show how Patsy's experiences fit with the bigger themes
that were found across all people. They also show how purpose, faith, and support are all linked
when it comes to building resilience and healing from childhood trauma.
A unique or unexpected code that emerged in Patsy's narrative is:
Temporal demarcation of responsibility: Patsy's clear distinction between her past and her
future offers an interesting perspective on how individuals can reframe their experiences and
take control of their lives.
Tachianna
The process of Tachianna healing and taking back control of her life is deeply connected
to her search for a sense of purpose and meaning. Tachianna showed perseverance by gradually

119
taking control of her situation in spite of having endured terrible childhood trauma and abuse. As
she explains her change, "I stopped living as a victim; I had a gradual process of taking control
of my life, from standing up to my abusers to leaving harmful situations." This change in
viewpoint is an important turning point in Tachianna's life, as she starts to perceive herself as an
active participant in her own story rather than a survivor. Her role as a mother also reflects her
sense of purpose, which probably gave her great drive to end the cycle of violence and provide
her child a better life. Tachianna's efforts to learn and develop despite adversity are another
example of her tenacity and resolve. "I learned about domestic responsibilities from her partner's
mother," she writes, demonstrating her dedication to self-improvement and establishing a secure
home for her family. Tachianna's journey indicates a developing sense of purpose focused on
healing, self-empowerment, and possibly assisting others who have gone through similar
tragedies, even though her precise calling is not made clear.
Tachianna's story reveals several key codes that align with the broader themes of having
a sense of purpose and calling, receiving support from others, and personal transformation. The
prominent codes in Tachianna's story include:
Reclaiming control: Tachianna's statement about "living as a victim" and taking control of her
life demonstrates resilience.
Breaking the cycle: Her role as a mother provided motivation to break the cycle of abuse and
create a better life for her child.
Personal growth: Tachianna's efforts to learn domestic responsibilities from her mother in law
show her commitment to personal development.
Resilience: Her ability to take charge of her circumstances despite adverse childhood
experiences exemplifies resilience.

120
A unique or unexpected code that emerged in Tachianna's narrative is:
Gradual empowerment: Tachianna's process of taking control was described as gradual.
Alex
Alex's story reveals a strong connection to the broader themes identified in the study of
resilience among survivors of childhood trauma. His journey towards finding a sense of purpose
and calling is shown in his determination to overcome adversity. Despite a challenging
childhood, Alex demonstrated a strong drive to improve his life and find meaning. His purpose
first emerged in his academic pursuits, he shares, "I started focusing on my grades. In the 7th
grade, I had a goal. I had a focus... and I got great grades because I had a purpose, and I got into
Benson." Even in the midst of his adversity, Alex continued to seek opportunities for growth and
self-improvement, stating, "I was learning all these books and reading all these things about
Think and Grow Rich and I started going to church." This pursuit of knowledge and spiritual
growth indicates Alex's commitment to personal development and finding meaning in his life.
His sense of purpose also manifested in his professional aspirations, he shares, "I started hitting
sales goals and then the process of that I had I had decided I'm gonna go back and get my high
school diploma." Alex's ability to overcome adversity and develop personal growth evident in his
response to emotional hardship: "I went to the gym, and 6 months later I came out completely
shredded, I had lost 55 pounds I had gotten down into like these rippe abs, muscles and
shoulders." This transformation demonstrates Alex's resilience and his ability to find purpose and
direction even in challenging circumstances.
Alex's narrative reveals four key codes that align with the broader themes of having a
sense of purpose and calling, receiving support from others, and personal transformation.
The codes in Alex's story include:

121
Academic focus: Alex's purpose emerged through his dedication to improving his grades and
setting educational goals.
Self-improvement: His desire for knowledge through reading and attending church.
Physical transformation: His dramatic weight loss and body transformation illustrate his ability
to channel adversity into personal growth.
A unique or unexpected code that emerged in Alex's narrative is:
Physical transformation as a coping mechanism: Alex's response to emotional hardship by
dramatically changing his physical appearance offers an interesting perspective on how purpose
can manifest in unexpected ways and serve as a tool for managing trauma-related challenges.
Mike
Mike’s journey of resilience and healing was deeply rooted in his sense of purpose and
calling, which he found through his spiritual transformation. Mike's narrative reveals a profound
connection to the broader themes identified in the study of resilience among survivors of
childhood trauma. His spiritual awakening and subsequent life changes clearly demonstrate how
finding a sense of purpose can drive personal transformation and resilience. This is evident in
Mike's description of his pivotal moment: "After I met Jesus. You know I wanted to finish my
schooling, so I sort of dropped back in." This newfound sense of purpose motivated Mike to
complete his education and pursue personal growth, illustrating how a strong sense of calling can
provide direction and motivation for overcoming past challenges. Mike's story is deeply rooted
in his faith, which he credits for his healing and newfound ability to connect with others. He
views resilience as a product of the spiritual healing process, stating, "I think resilience is a
reflection of the therapy of healing that God takes you through to restore and bring well-being
where you're not." This viewpoint emphasizes how spiritual beliefs can offer a framework for

122
comprehending and overcoming trauma, which is highly consistent with the idea of faith in God
and His transformational power. Though not directly stated, Mike's emerging capacity to build
connections suggests the significance of supportive relationships in his journey of healing. His
shift from introversion to establishing meaningful relationships with others indicates that he has
cultivated a support network as a component of his healing journey. Mike shares this
transformation, stating, "I wouldn't label myself as an introvert anymore." I was a part of my
trauma, and my favorite part is that I can connect with people now where I couldn't. I can love
people now, whereas before I was completely shattered. In addition to showing Mike's
development as a person, this capacity to build deep connections also emphasizes the importance
of social support in the process of resilience.
Several key codes emerge from Mike's narrative:
Spiritual awakening: Mike's encounter with faith marked a pivotal moment in his life, providing
him with a new sense of direction and purpose.
Educational pursuit: His newfound sense of purpose motivated him to complete his education,
demonstrating how his calling extended to personal growth and development.
Resilience through faith: Mike views resilience as a product of the spiritual healing process,
illustrating how his faith became a source of strength and restoration.
Relational healing: His transformation from introversion to forming deep connections with
others highlights the interpersonal aspect of his healing journey.
A unique or unexpected code that emerged in Mike's narrative is:
Redefining resilience: Mike's perspective on resilience as a reflection of God's healing process
offers an interesting theological interpretation of psychological resilience, bridging spiritual and
mental health concepts.

123
Mikeila
Mikeila's path of self-discovery and recovery is intricately linked to her search for
meaning and purpose in life. Mikeila showed amazing resilience by always looking for ways to
make her life better, even though she had a very hard childhood and went through a lot of pain
and hardship, saying, "I just kept on never giving up." This determination pushed her to try out
different support systems and therapy methods, which were very important in forming her sense
of purpose. Mikeila says that therapy and support groups were very important in her healing
process, stating, "Lot’s of my support groups and my therapist stuff. It's good." One important
thing that has helped Mikeila find her meaning is her dedication to loving and understanding
herself. Including her "inner child that's hurt" and her "critical parent," she talks about learning to
love all of herself and says, "I've learned how to love them all." Being able to accept herself has
been a big part of her healing and has given her a reason to keep growing as a person. Mikeila's
friendship with Christ has grown over the past few years, giving her more direction. She said, "I
just feel like I have another person to talk to that I can trust and that cares about me." This
spiritual link has given her a new sense of purpose and help on her ongoing path to healing and
self-discovery. Mikeila's story reveals several key codes that align with the three main themes of
having a sense of purpose and calling, receiving support from others, and faith in God and His
transformative power.
The codes in Mikeila's story include:
Resilience: Mikeila's determination to "never give up" demonstrates her remarkable resilience.
Support systems: Her reliance on support groups and therapy as significant factors in her healing
journey.

124
Self-love and understanding: Mikeila's commitment to loving all parts of herself, including her
"inner child" and "critical parent," shows a deep level of self-acceptance and personal growth.
A unique or unexpected code that emerged in Mikeila's narrative is:
Holistic self-acceptance: Mikeila's approach to loving all parts of herself, including those
typically seen as negative (like the "critical parent"), offers an interesting perspective on self-
love and healing.
Vikki
Vikki's narrative reveals a connection to the broader themes identified in the study of
resilience among survivors of adverse childhood experiences. Vikki's sense of purpose and
calling emerges as a complex journey shaped by her experiences of adoption, abuse, and faith.
Despite facing significant challenges, Vikki found a sense of purpose through her religious
upbringing and her role as a minister's wife. She reflects on the influence of her early religious
experiences, stating, "As a child, I was greatly influenced by the good religious leaders we were
constantly surrounded by." This religious foundation provided Vikki with a framework for
understanding her life and experiences. Her sense of purpose was further solidified through her
marriage and role as a minister's wife, as she shares, "due to the fact that she was raised in the
manner in which one is expected to be a wife, she became a minister's wife and became the
helpmate." While this role gave her a sense of direction, it also presented challenges in
recognizing and addressing neglect and abuse. Vikki's journey towards forgiveness and
understanding, particularly regarding her biological parents, also reflects her evolving sense of
purpose. She states, "I've come to terms with the fact that my father will never pick me over his
drug use," demonstrating her ability to find meaning and growth even in difficult relationships.
Vikki's resilience and her ability to maintain a 40-year marriage and raise three children, despite

125
her challenging background, further illustrate how her sense of purpose has guided her life
choices and helped her overcome adversity.
Vikki's narrative reveals several key codes that align with the three main themes of
having a sense of purpose and calling, faith in God and His transformative power, and personal
transformation. The codes in Vikki's story include:
Religious foundation: Vikki's early exposure to religious leaders significantly shaped her
worldview and provided a framework for understanding her experiences.
Role-based purpose: Her role as a minister's wife gave her a sense of direction and purpose,
albeit with its own challenges.
Forgiveness and acceptance: Vikki's journey towards forgiving and understanding her
biological parents demonstrates her evolving sense of purpose and personal growth.
Resilience through adversity: Her ability to maintain a long-term marriage and raise children
despite her challenging background illustrates her resilience.
A unique or unexpected code that emerged in Vikki's narrative is:
Dual nature of role-based purpose: While Vikki's role as a minister's wife gave her a sense of
direction, it also presented challenges in recognizing and addressing neglect and abuse. This
highlights the complex nature of finding purpose through societal or religious roles, which can
both empower and constrain individuals.
Support From Others
The theme of support from others is a critical factor in the resilience and healing
processes of individuals who have faced significant childhood trauma and adversity. The stories
of Dale, Camille, Mike, Patsy, Mikeila, Alex, Tachianna, and Vikki illustrate the significant
impact of diverse support systems, including family, friends, mentors, religious leaders, and

126
professionals, in their capacity to navigate challenges and foster resilience. This support
frequently functioned as a crucial resource, offering comfort, guidance, and strength in their most
challenging times. The presence of supportive others consistently emerges as an important factor
in the experiences of these individuals journeys from trauma to healing, regardless of whether it
took the shape of a caring therapist, a network of peers, a loving grandmother, or a
compassionate preacher. Their experiences demonstrate how outside assistance may improve
internal resilience by providing fresh viewpoints, coping mechanisms, and the vital reminder that
they are not facing their challenges alone.
Dale
Dale's narrative reveals a profound connection to the broader themes identified in the
study of resilience among survivors of adverse childhood experiences. Support from others
played a big role in Dale's journey of strength and healing, especially after he made the important
choice to leave his abusive home situation. Support from other people was very important in
helping Dale get over his terrible events and start a new life. After leaving home, Dale met a kind
preacher who became one of the most important people in his life who helped him. Dale says,
"There was a pastor there who didn't know all of the situation but was so fatherly, you know, and
compassionate to all of us." Finding a father-like figure who cared about him and supported him
was very important for Dale, especially since his own parents had betrayed him. Even though the
minister didn't know everything about Dale's situation, his kindness made the church a safe and
caring place for Dale. Dale also stresses how important it is to have helpful people around him
who can understand what he's going through and help him get better. "I needed people around
me who had been there," he says. There should be people in my life who believe in me as a

127
person. In this case, it shows that Dale knew that surrounding himself with understanding and
helpful people was important for his healing.
Dale's story reveals several key codes that align with the three main themes of receiving
support from others, having a sense of purpose and calling, and faith in God and His
transformative power. The codes in Dale's story include:
Supportive mentorship: The compassionate pastor who provided a father-like figure for Dale
played a crucial role in his healing process.
Peer support: Dale's emphasis on surrounding himself with people who had similar experiences
highlights the importance of relatable support networks.
Faith-based healing: The involvement of a pastor in Dale's journey suggests the role of faith in
his recovery process.
Leaving toxic environments: Dale's decision to leave his abusive home environment marks a
significant turning point in his journey towards healing.
A unique or unexpected code that emerged in Dale's narrative is:
Selective vulnerability: Dale's mention that the pastor didn't know all of his situation, yet still
provided crucial support, suggests an interesting dynamic of receiving help without full
disclosure. This highlights the importance of safe spaces where individuals can receive support
even without sharing their entire story.
Patsy
Patsy's story reveals a connection to the broader themes identified. Patsy talked about
how important it was for her to have outside help during her hard childhood. "I could run away
to school," she said. I had friends in the area. These relationships gave her a safe place to go
when things at home got tough and helped her deal with problems. Even though she couldn't do

128
everything, Patsy's mother tried to keep her safe from abuse. Even though this early help wasn't
perfect, it made Patsy feel like someone cared about her well-being. But Patsy's inner strength
and ability to rely on herself were the most important things that helped her in her early life.
Then she says, "Self-reliance. There are both good and bad things about my pride. I knew I didn't
deserve what was happening to me and that the adults in my life were definitely not in charge of
their money. As an adult, Patsy also got help from the people she was close to. According to her,
when she's feeling stressed, she talks to her husband or accountability partner: "I journal... I
talked to my husband or my accountability partner." These relationships help her feel better and
give her a safe place to work through her feelings and thoughts. The support Patsy got from her
faith group was also very important in her healing process. "Every once in a while he gives me
these revelations," she shared that one of the revelations that helped her make sense of her events
and take charge of her life when she told herself “Okay, I am 18 years old. I'm by myself. What
happened before is my parents' fault.”
Patsy's story reveals several key codes that align with the three main themes of receiving
support from others, having a sense of purpose and calling, and faith in God and His
transformative power. The codes in Patsy's story include:
External support systems: Patsy's mention of school and neighborhood friends as escape routes
demonstrates the importance of supportive relationships outside the home.
Maternal protection: Despite limitations, Patsy's mother's attempts to protect her provided a
sense of care and support.
Self-reliance: Patsy's emphasis on her inner strength and self-reliance as coping mechanisms
highlights her resilience.

129
Adult support networks: Her references to her husband and accountability partner show the
importance of supportive relationships in adulthood.
Faith-based support: Patsy's experiences with divine revelations illustrate the role of spiritual
support in her healing journey.
A unique or unexpected code that emerged in Patsy's narrative is:
Pride as a double-edged sword: Patsy's acknowledgment of pride as "a negative as well as a
positive" offers an interesting perspective on how personal traits can be both beneficial and
challenging in the healing process.
Mike
Mike's story reveals a connection to the broader themes. Mike discussed how his healing
journey involved learning to connect with others in a meaningful way. Despite growing up in a
challenging home environment marked by parental abuse and addiction, Mike found strength and
transformation through the support he received from others, particularly in his spiritual
community. Mike’s early life was characterized by a lack of positive support. He describes his
family situation, saying, "My mom struggled with alcoholism, and my dad dealt with military
PTSD." This unstable home environment was further compounded by abuse, as Mike shares,
"my mom and dad were abusive." The absence of supportive parental figures left Mike
vulnerable to further trauma, including molestation by a babysitter. However, Mike's life took a
significant turn when he encountered supportive individuals through his faith community. He
marks this as a pivotal moment in his journey, stating, "After I met Jesus. You know I wanted to
finish my schooling, so I sort of dropped back in." This support not only motivated Mike to
complete his education but also provided a framework for healing and personal growth. The
impact of this support is further illustrated in Mike's description of his personal growth. He

130
shares, "I wouldn't call myself an introvert anymore. That it was a part of my trauma," and "the
favorite part is that I can connect with people now where I couldn't. I can love people now, and
where before I was utterly broken."
Mike's story reveals several key codes that align with the three main themes of receiving
support from others, personal transformation, and faith in God and His transformative power.
The prominent codes in Mike's story include:
Spiritual awakening: Mike's encounter with faith marked a significant turning point in his life,
providing him with a new sense of direction and support.
Educational pursuit: His newfound sense of purpose motivated him to complete his education,
demonstrating how support can lead to tangible life improvements.
Relational healing: Mike's transformation from introversion to forming deep connections with
others highlights the interpersonal aspect of his healing journey.
A unique or unexpected code that emerged in Mike's narrative is:
Introversion as a trauma response: Mike's description of his former introversion as "part of my
trauma" offers an interesting perspective on how childhood adversity can shape personality and
social behavior. This insight adds depth to our understanding of the long-term effects of trauma
and the potential for healing and change.
Tachianna
Tachianna’s story reveals a profound connection to the three main themes. Tachianna's
journey of resilience and healing was significantly influenced by the support she received from
others, despite the severe trauma and abuse she experienced throughout her childhood and early
adulthood. While her story is marked by numerous instances of betrayal and harm from those
who should have protected her, there were also key moments and relationships that provided

131
crucial support. One of the most significant sources of support for Tachianna was her
relationship with her biological brother. Even in their earliest memories of foster care, this bond
provided a sense of stability and comfort. Tachianna recalls "crying in a crib around age 2 and
moving through various foster homes" with her biological brother, highlighting the importance
of their connection amidst the chaos of their early lives. This sibling relationship served as a
constant source of support throughout her tumultuous childhood. Tachianna shared how finding
supportive individuals later in life helped her begin to heal from her childhood trauma. She
mentioned a compassionate pastor who provided fatherly support: "There was a pastor there who
didn't know all of the situation but was so fatherly you know, compassionate to all of us.” This
experience of compassionate spiritual guidance likely played a significant role in her healing
process.
Tachianna's story reveals several key codes that align with the broader themes of
receiving support from others, resilience, and personal transformation. The codes in Tachianna's
story include:
Sibling support: Tachianna's bond with her biological brother provided a crucial source of
stability and comfort throughout her challenging childhood.
Gradual empowerment: Tachianna's process of healing and reclaiming control over her life was
described as a gradual progression.
A unique or unexpected code that emerged in Tachianna's narrative is:
Early memory of trauma: Tachianna's vivid recollection of "crying in a crib around age 2 and
moving through various foster homes" provides insight into the long-lasting impact of early
childhood trauma and the importance of consistent support from a young age.
Alex

132
Alex’s story reveals a profound connection to the broader themes. Despite his difficult
upbringing, the support he received from others had a big impact on his path to recovery and
resilience. Even though Alex had a pretty rocky start with a lot of ups and downs, he managed to
find some solid support that really helped him grow and change for the better. One of the first
ways Alex felt supported was through the sense of community in his neighborhood, even with its
ups and downs. He remembers, "there was a ton of fun at Carlton Court, too." We swung on the
swings. We swung on the swings, rode our bikes, and just cruised around town on our own,
exploring everything. Alex found some good times and a sense of connection with other kids,
which made things a bit brighter despite the tough stuff going on. As Alex got older, he
discovered that educational opportunities really helped him out and kept him motivated. He says,
"I began to pay more attention to my grades." Back in 7th grade, I set a goal for myself.
Alex's story reveals several key codes that align with theObroader themesOof receiving
support from others, personal transformation, andOdeveloping a sense of purpose. The codes in
Alex's story include:
Educational opportunities: School became a source of support and motivation for Alex, offering
him a sense of purpose and direction.
Self-directed learning: Alex's pursuit of self-help books and personal development resources
demonstrates his proactive approach to seeking support and growth.
A unique or unexpected code that emerged in Alex's narrative is:
Physical transformation as a coping mechanism: Alex's response to emotional hardship by
dramatically changing his physical appearance offers an interesting perspective on how purpose
and resilience can manifest in unexpected ways.
Camille

133
Camille’s story reveals a profound connection to the broader themes identified in the
study of resilience among survivors of childhood trauma. Despite the terrible things that
happened to her as a child, the help she received from others played a big role in her ability to
heal and become strong. In her early years, Camille was abused and betrayed by people who
were supposed to protect her. As she got older, she found important support in many
relationships and groups. Camille's faith group was one of the most important places where she
could get help. There aren't any specifics about the people she healed, but it's clear that her
Christian faith was very important to her. Camille was able to forgive her abusers because of her
strong religious views. "I would have still been able to tell him, 'I forgive you like God
forgives,'" she says. "But he just throws it into the sea of forgetfulness." I'm not going to talk
about that with you ever again. I will forgive you, though. Camille's early life was marked by
terrible trauma and a lack of support. Her faith group, her marriage, and maybe even professional
help gave her the support she needed.
Camille's story reveals several key codes that align with the broader themes of receiving
support from others, faith in God and His transformative power, and personal transformation.
The codes in Camille's story include:
Faith-based forgiveness: Camille's ability to forgive her abusers was deeply rooted in her
religious beliefs, demonstrating how her faith provided a framework for healing.
Marital support: Camille's transformation in her approach to intimate relationships suggests that
her marriage provided a supportive environment for healing and growth.
A unique or unexpected code that emerged in Camille's narrative is:
Reinterpretation of intimacy: Camille's specific mention of reinterpreting "what a healthy,
loving, sexual relationship was all about" offers an interesting perspective on how healing can

134
transform one's understanding and experience of intimate relationships. This highlights the
profound impact that trauma can have on all aspects of life and the potential for healing to
reshape these experiences.
Mikeila
Mikeila’s story reveals a connection to the broader themes identified in the study of
resilience among survivors of childhood trauma. Despite the difficult and traumatic events she
went through as a child and young adult, Mikeila's journey of resilience and healing was greatly
impacted by the support she received from others. Mikeila's grandma was one of the first and
most important people who helped her. When Mikeila talks about the resources she had as a
child, she says, "Well, I didn't really have any resources other than Grandma Susan." As Mikeila
got older, she got help from different types of therapy and support groups. "A lot of my support
groups and my therapist stuff," she says, naming them as important parts of her healing process.
It's good. This shows how important professional mental health help and support from peers are
for people who have been through traumatic events as children to get better. I think Mikeila also
found support in gymnastics, even though she knows it has its limits. She says, "I did use my
gymnastics a lot to distract myself, but it didn't really do anything for me, as far as resources,
though you know what I mean, like." Even though it didn't give Mikeila a lot of emotional
support, this activity gave her a short break and a sense of success, which can be helpful for kids
who are having a hard time. In the past few years, Mikeila's growing bond with Christ has given
her more support. "I just feel like I have another person to talk to that I can trust and that cares
about me," she says about this new source of comfort. Mikeila's story reveals several key codes
that align with the broader themes of receiving support from others, personal transformation, and
faith in God and His transformative power. The codes in Mikeila's story include:

135
Professional help: Her involvement in therapy and support groups played a significant role in
her healing journey.
Coping mechanisms: Mikeila's use of gymnastics as a distraction, though limited in its
effectiveness, served as a temporary coping strategy.
A unique or unexpected code that emerged in Mikeila's narrative is:
Limited effectiveness of distraction: Mikeila's insight about gymnastics providing distraction but
not deep healing offers an interesting perspective on the limitations of certain coping
mechanisms.
Vikki
Vikki’s story reveals a connection to the broader themes identified in the study of
resilience among survivors of childhood trauma. The help Vikki received from those around her
had a big impact on her ability to bounce back and heal. The religious leaders in Vikki's group
were one of the first people who helped her. She says, "As a child, I was greatly influenced by
the good religious leaders we were constantly surrounded by." Though, Vikki's time with her
new family was more complicated. Being adopted could have been a source of comfort, but it
turned out to be even worse. "There was abuse in the home, including abuse of the mind, body,
and emotions," Vikki says. I knew it was happening, but I didn't know it was abuse. In later
years, Vikki's religion and her job as the wife of a minister helped her keep going. She says, "due
to the fact that she was raised in the manner in which one is expected to be a wife, she became a
minister's wife and became the helpmate."
The theme of help from others stands out as an important part of how people who have
been through adversity as children are able to bounce back and heal. We can see how different
kinds of help from family, friends, mentors, religious leaders, and professionals had a big effect

136
on the people we interviewed as they worked to overcome problems and become more resilient.
The people who took part said that spiritual support and faith groups were important sources of
strength. These stories show the different kinds of help and how important it is for building
resilience. The authors stress that the process of healing from a traumatic event in childhood is
very personal, but that the help one gets from others can often shape that process. Support can
come in many forms and at different times in a person's life, but it is always very important for
healing and personal growth. Support from Others is a theme that stresses that healing and
resilience are not things that people do by themselves. Instead, they are deeply connected to the
relationships and support systems that people have throughout their lives. These stories show
how important it is to create safe and helpful places and people for kids and adults who have
been through trauma. They show that with the right help, people can not only get through tough
times but also thrive.
Vikki's story reveals several key codes that align with the three broader themes of
receiving support from others, faith in God and His transformative power, and personal
transformation. The prominent codes in Vikki's story include:
Complex adoption experience: While adoption could have been a source of support, it instead
became a source of further trauma for Vikki.
Role-based purpose: Her role as a minister's wife gave her a sense of direction and purpose,
albeit with its own challenges.
A unique or unexpected code that emerged in Vikki's narrative is:
Dual nature of adoption: Vikki's experience highlights how adoption, typically seen as a
positive support system, can sometimes be a source of further trauma. This adds complexity to
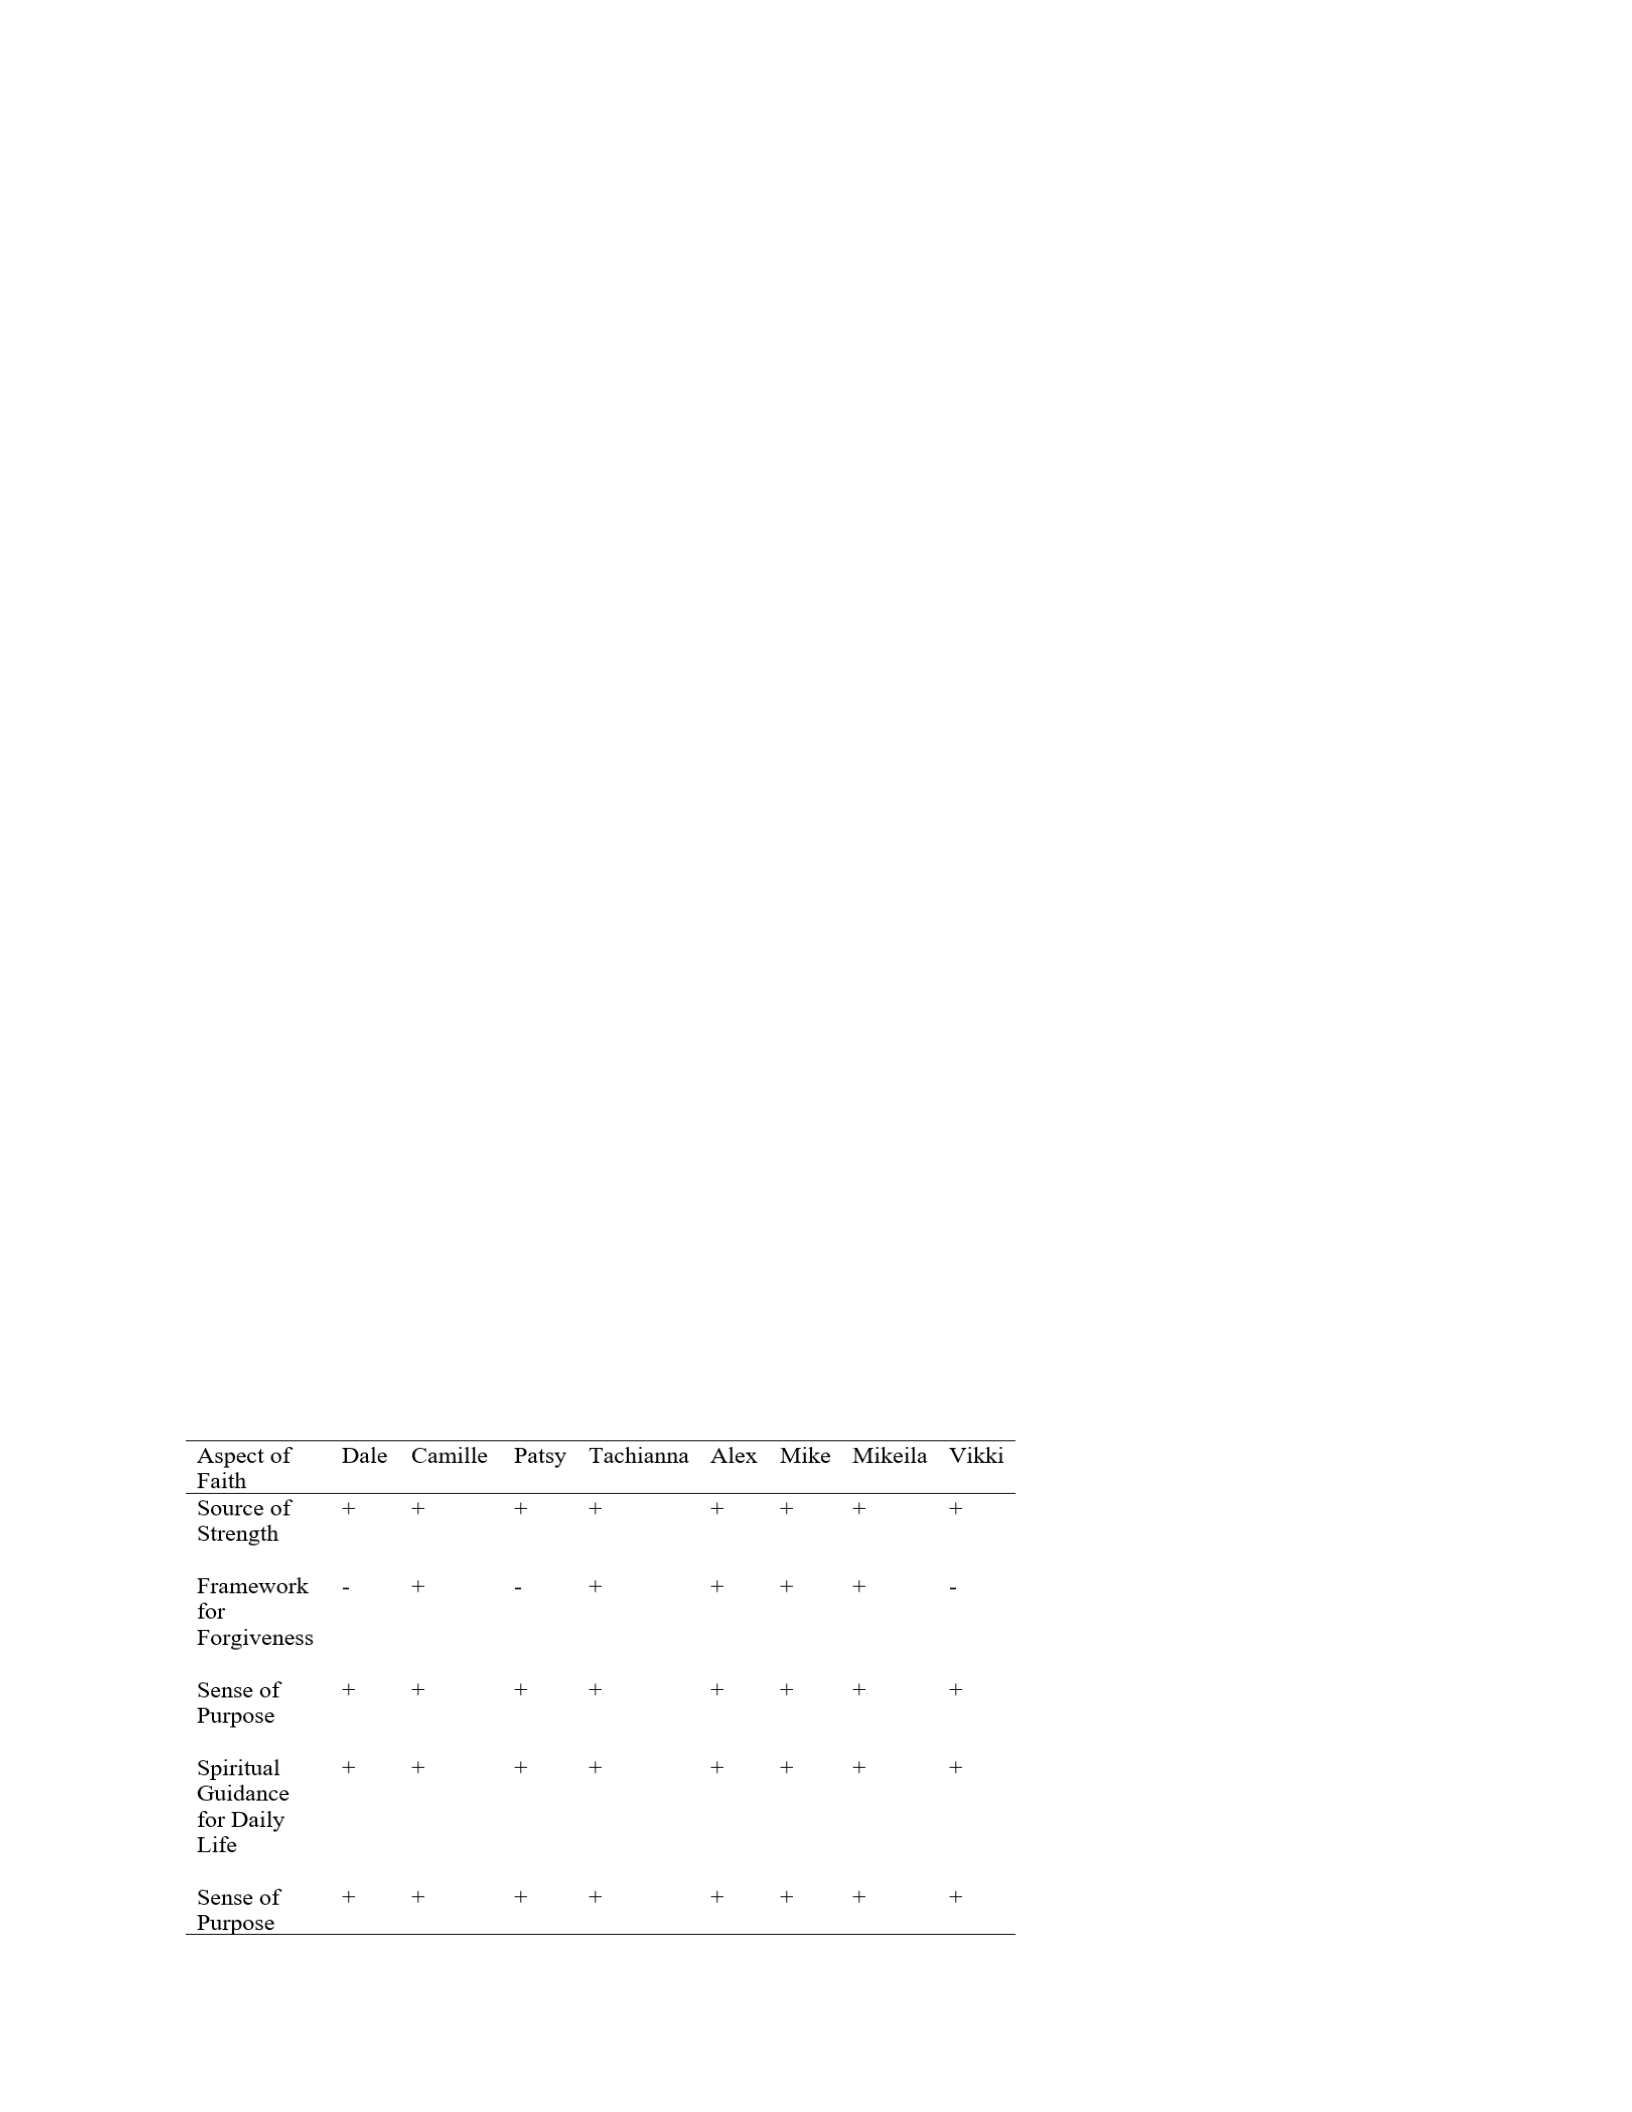
137
our understanding of family dynamics and support systems in the context of childhood trauma
and resilience.
Faith in God
Individuals who have experienced significant childhood trauma and hardship often find
that their faith has a profound and life-altering impact on their lives. The stories of Dale,
Camille, Michael, Tachianna, Patsy, Mikeila, Vikki, and Alex reveal that faith serves as a crucial
component of resilience, providing strength, guidance, and a framework for enduring challenges.
For these survivors, faith transcends mere religious belief, representing a deep-seated trust in a
higher purpose and the possibility for individual growth and transformation. It acts as an
incentive for change, offering comfort in difficult times, motivation to persevere, and a structure
for reevaluating troubling experiences. the ability to not only withstand challenges but thrive.
Examining their narratives reveals how their faith interacts with their resilience journeys,
impacting their coping mechanisms, forming their viewpoints, and eventually helping them not
only endure but flourish in the face of hardship. The influence of faith was profound in the
resilience and healing journeys of all of theOparticipants.
Table 4
Aspects of Faith

138
Mike
Mike stressed the importance of his faith and relationship with God in his recovery. He
expressed, "In Christ he binds the wounds, and then he brings healing." Michael regarded
resilience as a manifestation of "the therapy of healing that God guides you through to restore
and bring well-being." For him, faith served as a foundation for comprehending and transcending
trauma. Mike's story reveals several key codes that align with the three themes of faith in God
and His transformative power, personal transformation, and developing a sense of purpose. The
codes in Mike's story include:
Divine therapy: His view of resilience as a reflection of God's healing therapy highlights the
spiritual dimension of his healing journey.
Faith in God and His transformative power: Mike's narrative is deeply rooted in his belief that
God was the primary source of his healing and resilience. This aligns strongly with the theme of
faith as a transformative force in overcoming trauma.
Personal transformation: Mike's journey from being "utterly broken" to forming deep
connections with others demonstrates significant personal growth and resilience, directly linked
to his spiritual transformation.
Developing a sense of purpose: Mike's newfound ability to connect with and love others became
a central part of his purpose, illustrating how his calling emerged from his healing journey.
A unique or unexpected code that emerged in Mike's narrative is:
Resilience as divine therapy: Mike's interpretation of resilience as a reflection of God's healing
process offers an interesting theological perspective on psychological resilience, bridging
spiritual and mental health concepts in a novel way.
Tachianna

139
Growing up, Tachianna experienced a "very religious background" that she described as
"very cultish." This implies that rather than easing her trauma, her early encounters with
organized religion may have been damaging or constrictive. Her relationship with faith and
spirituality during her formative years was probably hampered by such an environment. Later in
life, Tachianna managed to reestablish a more positive connection with her faith in spite of these
difficult early experiences. She mentioned a caring preacher who offered encouragement, which
demonstrates this shift in her spiritual path. Instead of adding to Tachianna's pain, this
experience seemed to have given her a glimpse of how faith and religious leaders could be
consoling and uplifting. Tachianna's story reveals several key codes that align with the broader
themes of religious trauma, personal transformation, and finding support through faith. The
prominent codes in Tachianna's story include:
Religious trauma: Tachianna's description of her upbringing as "very religious" and "very
cultish" indicates early experiences of religious trauma. These codes connect to the broader
themes in the following ways:
Religious trauma and its impact: Tachianna's early experiences align with the concept of
religious trauma syndrome, where authoritarian or controlling religious environments can lead to
long-lasting psychological effects.
A unique or unexpected code that emerged in Tachianna's narrative is:
Partial disclosure as a pathway to support: Tachianna mentions that the pastor "didn't know all
of the situation," yet was still able to provide meaningful support. This suggests that complete
vulnerability may not always be necessary for individuals to receive beneficial spiritual guidance
and support.
Mikeila

140
Mikeila's story has a deep link to the larger themes found in the study of resilience among
people who have been through traumatic events as children. Her growing friendship with Christ
shows how faith can help people heal by giving them more direction and support. Mikeila says,
"I just feel like I have another person to talk to that I can trust and that cares about me." This
spiritual link has become a big source of comfort and guidance for her. This personal and
relational part of Mikeila's faith fits in well with the idea of faith in God and His power to change
things. It shows how spiritual beliefs can help people understand and get over trauma. Mikeila's
journey of healing and self-improvement includes her faith, which shows how spiritual growth
can be an important part of total personal change. Her dedication to loving and understanding
herself, along with her new spiritual link, shows that she has grown and changed a lot. The fact
that Mikeila has learned to love all of herself, even her "inner child that's hurt" and her "critical
parent," shows that she has a deep understanding of herself that has been essential to her
recovery. This method of personal growth that includes both psychological and spiritual aspects
shows how resilient and recoverable people are from childhood trauma. Mikeila's story reveals
several key codes that align with the broader themes of faith in God and His transformative
power, personal transformation, and developing a sense of purpose. The codes in Mikeila's story
include:
Self-love and understanding: Her commitment to loving all parts of herself, including her "inner
child" and "critical parent," shows a deep level of self-acceptance and personal growth.
Camille
The theme of faith stands out as a significant influence in Camille's path toward healing
and resilience. Her religious beliefs offered a structure for comprehension, forgiveness, and
personal development amidst significant childhood trauma. Camille’s faith significantly

141
influenced her capacity to forgive her abusers, especially her father. She articulates this feeling
with great intensity, saying, "I would have still been able to say to him, I forgive you like God
forgives... and he throws it in the sea of forgetfulness... I'm not gonna bring that up to you ever
again." However, I have decided to forgive you. This act of forgiveness, inspired by her
comprehension of divine forgiveness, marked a crucial milestone in her healing journey,
enabling her to let go of the weight of anger and resentment. Additionally, Camille's faith played
a crucial role in aiding her to navigate the enduring impacts of abuse on her personal
relationships. She reflects on the transformative impact of her spiritual journey, stating, "I didn't
really recognize that I still had some real sexual issues until after I became a Christian." This
understanding initiated a healing journey that was profoundly connected to her faith. Camille
explains, "It wasn't until I allowed God to heal me and to redefine what a healthy, loving, sexual
relationship meant that I could truly relax and enjoy being with my husband in that way." This
statement highlights how her faith offered a way to reshape and mend her perception of intimacy.
Camille's story reveals several key codes that align with the broader themes of faith include:
Faith-based forgiveness: Camille's ability to forgive her abusers was deeply rooted in her
religious beliefs, demonstrating how her faith provided a framework for healing.
Spiritual healing: Her journey of overcoming the effects of abuse on her intimate relationships
was intrinsically linked to her faith and spiritual growth.
Redefining intimacy: Camille's process of reinterpreting and healing her understanding of
healthy sexual relationships through her faith highlights a unique aspect of her transformation.
Breaking generational patterns: While not explicitly mentioned in this excerpt, Camille's
commitment to open communication with her children suggests a determination to end cycles of
abuse and secrecy.

142
A unique or unexpected code that emerged in Camille’s narrative is:
Faith as a trusted confidant: Mikeila's description of Christ as "another person to talk to that
that I can trust, that cares about me" presents faith not just as a belief system, but as a personal,
trusting relationship. This perspective adds depth to our understanding of how faith can function
as a source of support and comfort for individuals recovering from trauma.
Dale
These codes connect to the broader themes in the following ways. Resilience,
transformation, and a strong dependence on God amidst terrible childhood trauma and tragedy
are hallmarks of his spiritual path. His faith was instrumental in his healing journey and personal
development, offering him strength, purpose, and a way to comprehend his experiences. Dale's
faith journey commenced during his childhood, nurtured in a Christian household. Nevertheless,
this belief faced significant challenges due to the harrowing experiences he went through. In
spite of the hardships he endured, Dale discovered resilience in his convictions. He expressed, "I
just knew that I had faced many challenges, yet I continued to rise, remained steadfast, and was
still being utilized by God." This statement illustrates Dale's strength and his conviction that
there was a divine purpose for his life, even during his times of hardship. Dale's life clearly
illustrates the profound impact of faith, as it has significantly influenced his outlook on both his
past experiences and his future possibilities. At a pivotal moment in his life, Dale made a choice
that was profoundly shaped by his faith: "when I was 14 and a half." Dale's story reveals several
key codes that align with the three broader themes of faith in God and His transformative power,
support in the community, and developing a sense of purpose. The codes in Dale's story include:
Faith-driven resilience: Dale's ability to endure and overcome severe childhood trauma was
deeply rooted in his belief that God had a purpose for his life.

143
Spiritual strength: His statement about getting back up after "a lot of hits" and still being used
by God demonstrates how his faith provided him with inner strength.
Transformative decision-making: Dale's faith-influenced decision to leave home at 14 and a
half marks a critical turning point in his journey towards healing.
Purpose through adversity: Despite his traumatic experiences, Dale maintained a belief that God
was using him, indicating a sense of divine purpose.
A unique or unexpected code that emerged in Dale's narrative is:
Faith-driven action: Dale's decision to leave home at a young age, influenced by his faith,
highlights how spiritual beliefs can empower individuals to take decisive actions for their well-
being, even in challenging circumstances.
Alex
Alex's narrative reveals a profound connection to the broader themes identified in the
study of resilience among survivors of adverse childhood experiences. Alex's journey of faith
becomes clear as a key part of his strength and growth as a person. His early life was full of
terrible hardships and pain, but when he found faith later in life, it helped him start to heal.
Alex's conversion to Christianity seems to have happened at the same time as a time of personal
growth and improvement. Alex's journey of faith also seems to have made him stronger and
better able to deal with problems. For example, when he was depressed after a breakup, he used
his energy to improve himself. Even though he changed physically, it's likely that his growing
faith gave him the mental and emotional strength to get through this hard time. Alex's story
reveals several key codes that align with the three broader themes of support from community,
faith in God, and finding a sense of purpose or calling. The prominent codes in Alex's story
include:

144
Personal growth through faith: Alex's introduction to church coincided with his efforts to
improve himself and find meaning in life.
Resilience through spiritual connection: His growing faith appears to have provided mental and
emotional strength during challenging times.
Self-improvement as a coping mechanism: Alex's response to emotional hardship by
transforming his physical appearance demonstrates his resilience and determination.
A unique or unexpected code that emerged in Alex's narrative is:
Physical transformation as a spiritual metaphor: Alex's dramatic physical change after
emotional hardship offers an interesting perspective on how faith and resilience can manifest in
tangible, physical ways. This transformation serves as a powerful metaphor for his inner spiritual
and emotional growth.
Patsy
Patsy's narrative reveals a profound connection to the broader themes identified in the
study of resilience among survivors of adverse childhood experiences. Patsy's journey of faith
becomes a main theme in her story of overcoming childhood pain and getting better. Through all
of her hard times, her faith has been a strong source of strength, direction, and comfort. It was a
big part of how she was able to get through them. Patsy found comfort in her faith from a very
young age and used it as a way to deal with the sexual abuse she was going through. As she got
older, her bond with God grew stronger. It became an important part of her daily life and how
she dealt with problems and stress. It's not enough for Patsy to just believe in God; she also acts
on her faith when she needs to. Patsy's daily habits and ways of dealing with stress show how
much she relies on her faith. She says, "Now, if I'm having my very best day, I take it to Jesus
first thing." This sentence shows that she puts her faith first in her life and that she looks for

145
spiritual direction and support before anything else. In addition to prayer, she reads and studies
the Bible as part of her faith. She uses these activities to improve herself and deal with stress.
Patsy's story reveals several key codes that align with the three broader themes of faith in God,
finding a sense of purpose or calling, and receiving support from others. The codes in Patsy's
story include:
Faith as a coping mechanism: Patsy uses her faith to deal with stress and challenges, turning to
God first in her daily life.
Spiritual practices: Her engagement in Bible study and reading demonstrates active participation
in her faith.
Resilience through faith: Patsy's ability to overcome severe adversities is closely tied to her
strong religious beliefs.
Spiritual guidance: She seeks direction and comfort from her faith, especially in difficult times.
A unique or unexpected code that emerged in Patsy's narrative is:
Faith as a proactive tool: Rather than turning to faith only in times of hardship, Patsy actively
incorporates her beliefs into her daily routine, even on her "best days." This proactive approach
to faith demonstrates how spiritual practices can be used not just for coping with difficulties but
also for maintaining and enhancing overall well-being.
Vikki
Vikki's narrative reveals a profound connection to the broader themes identified in the
study of resilience among survivors of adverse childhood experiences. Vikki's journey of faith is
deeply connected to her struggles with pain, her ability to bounce back, and her healing. It looks
like her faith was always there for her, helping her and giving her problems as she dealt with
complicated family issues and personal growth. Vikki was influenced by religion from a very

146
young age. She says, "As a child, I was greatly influenced by the good religious leaders we were
constantly surrounded by." This shows that her faith community had a big impact on how she
saw the world and was there for her when she was growing up. For Vikki, being around these
religious leaders probably gave her a sense of security and direction, especially since her early
life was so rough.
Vikki's story reveals several key codes that align with the three broader themes of support from
community, faith in God, and finding a sense of purpose or calling. The prominent codes in
Vikki's story include:
Early religious influence: Vikki's childhood exposure to religious leaders shaped her worldview
and provided a foundation for her faith.
Faith as a framework: Her religious upbringing offered a structure for understanding her life
experiences and challenges.
Role-based purpose: Vikki's position as a minister's wife gave her a sense of direction and
calling.
Resilience through faith: Despite facing significant adversity, Vikki's faith appears to have been
a source of strength and perseverance.
A unique or unexpected code that emerged in Vikki's narrative is:
Dual nature of faith-based roles: While Vikki's role as a minister's wife provided her with
purpose, it also presented challenges in recognizing and addressing neglect and abuse. This
highlights the complex nature of finding purpose through religious roles, which can both
empower and potentially constrain individuals in their personal growth and healing journeys.
In conclusion, for many participants, these survivors find that faith goes beyond simple
religious belief; it embodies a profound trust in a higher purpose and the potential for personal
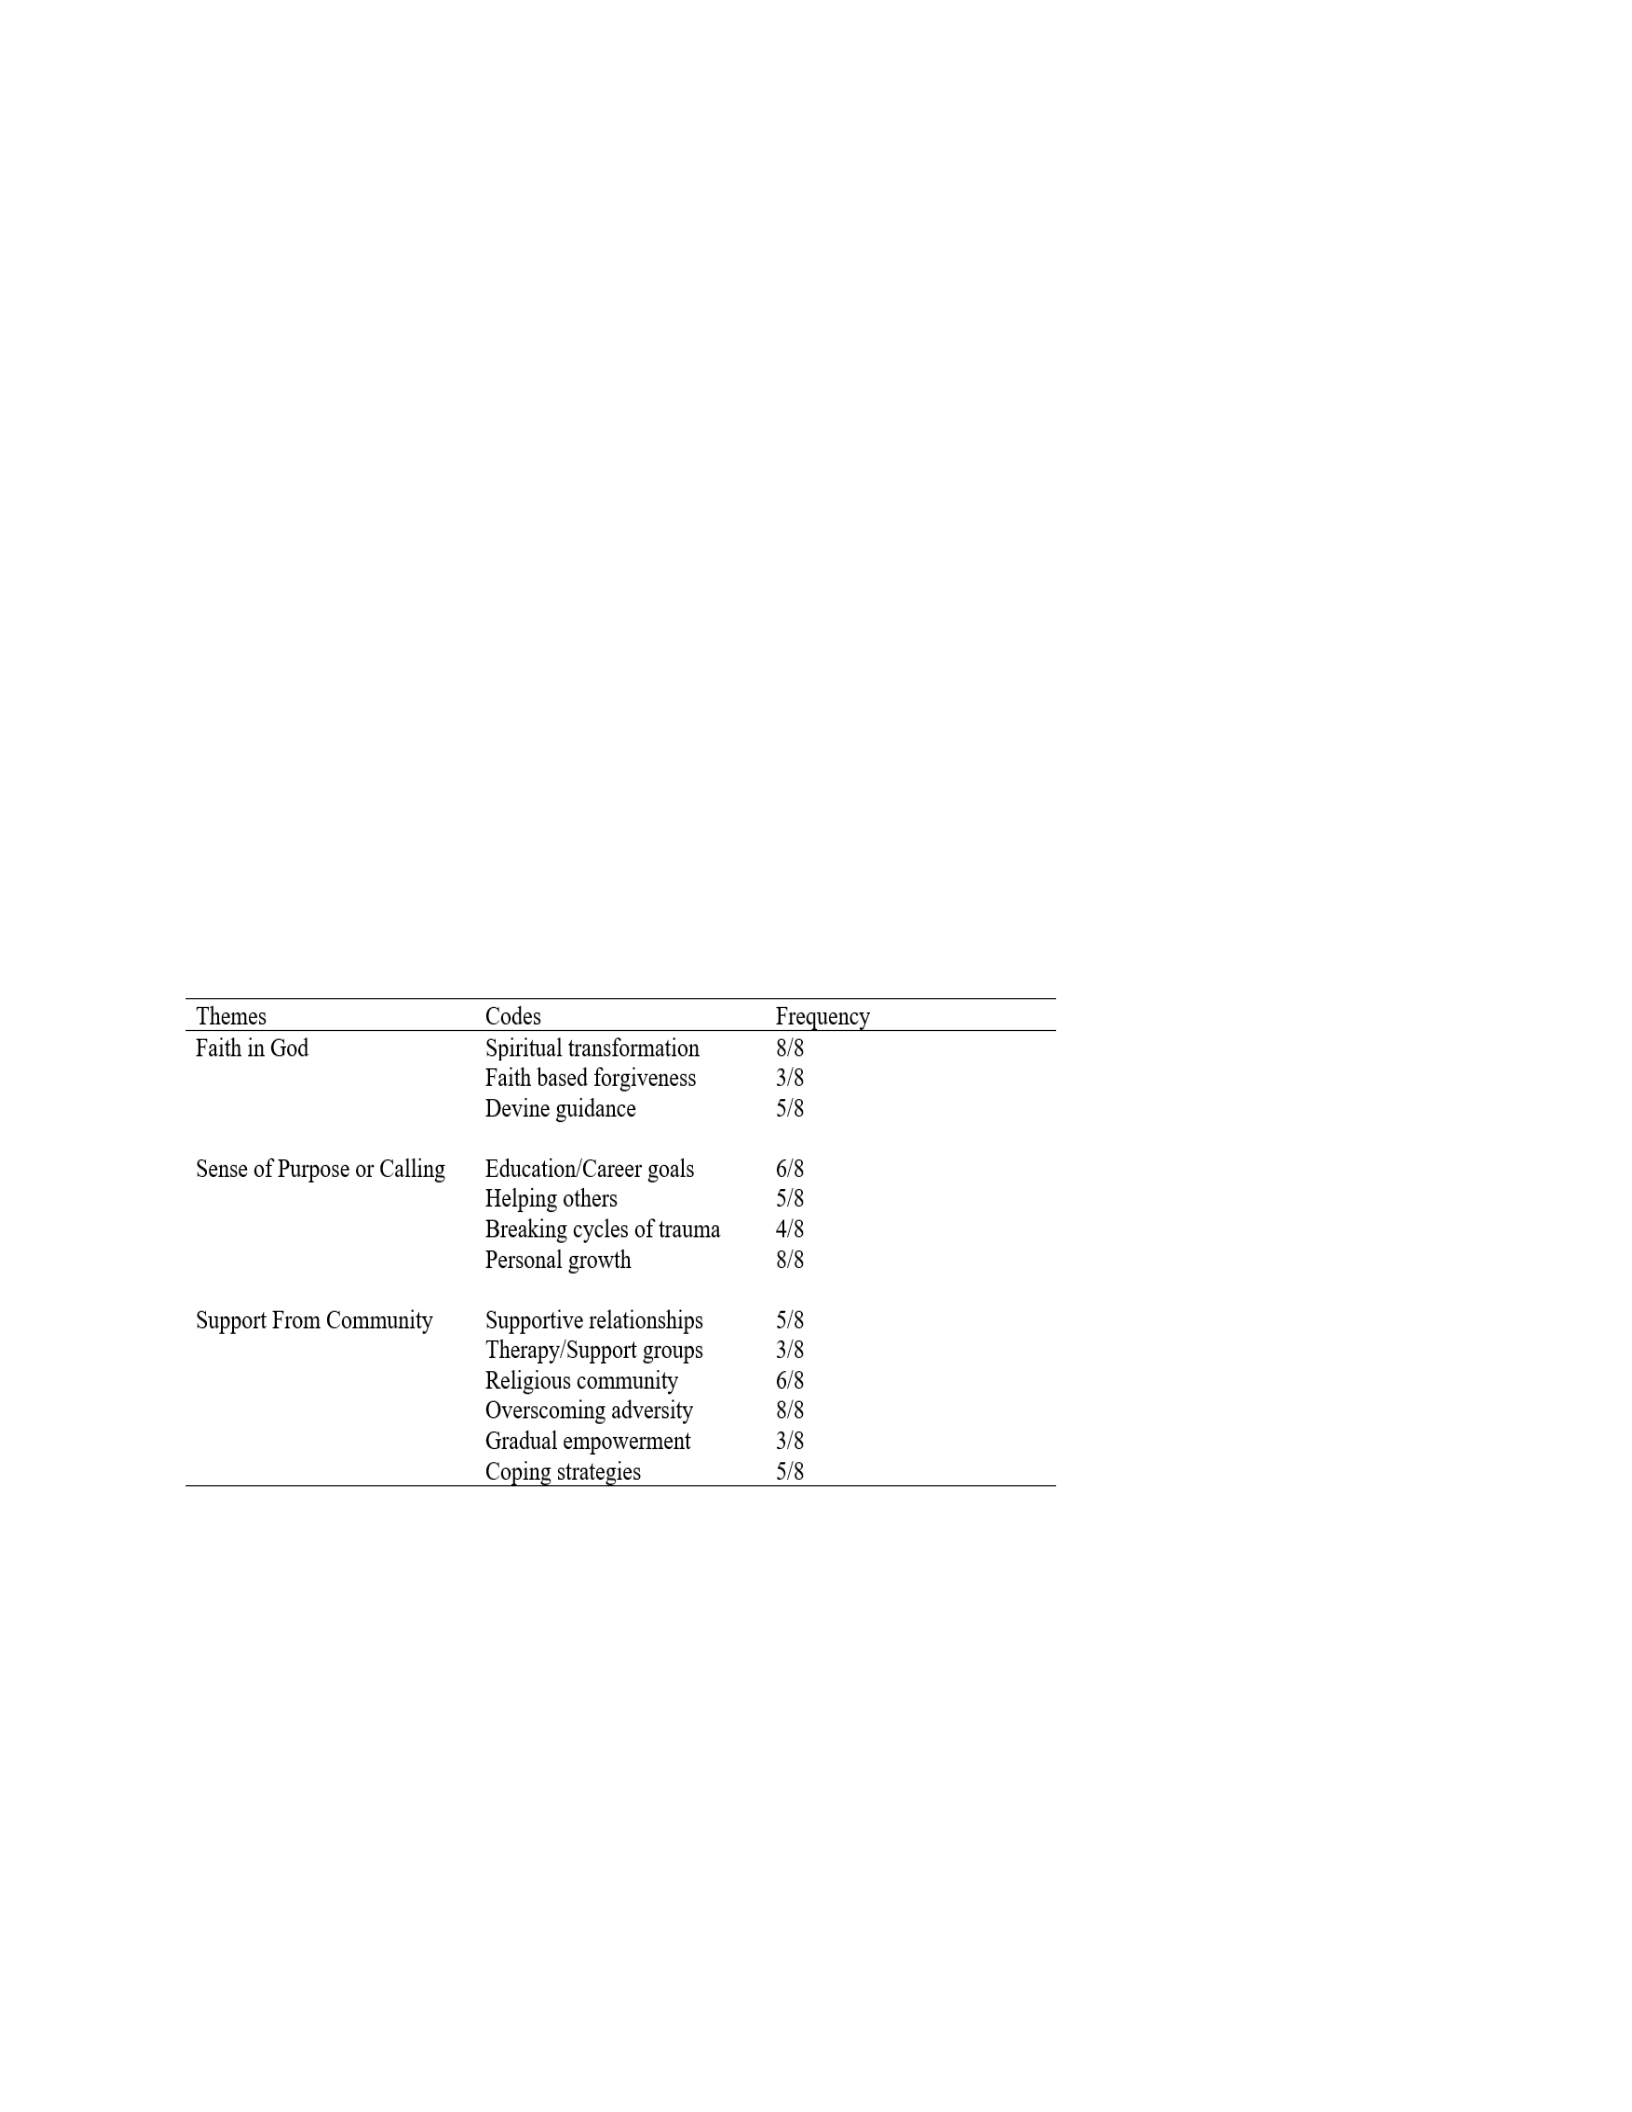
147
growth and redemption. It serves as a driving force for transformation, providing comfort during
challenging times, motivation to keep going, and a way to reframe difficult experiences. Faith
offers a structure for forgiveness, healing, and discovering purpose in life following trauma. It is
essential to recognize that faith experiences differed among participants. Some individuals, such
as Tachianna, navigated intricate relationships with organized religion because of challenging
early experiences. Some individuals, such as Mikeila, discovered faith later in their lives,
providing them with an extra layer of support. In summary, although not relevant to everyone,
faith played a crucial role in the resilience and healing journeys of many participants, offering
them strength, guidance, and a sense of purpose when confronted with challenges.
Table 5
Themes and Codes
Research Question Responses
The responses from the semi-structured interview were transcribed and analyzed, leading
to the identification of threeOthemes that correspond to the research questions guiding this study.
The following section explores the significant responses provided by participants.

148
RQ1: How do adults who experienced childhood trauma describe the essence of their lived
experiences?
Based on the interview data collected, adults who experienced childhood trauma describe
the essence of their lived experiences through several key themes: resilience and healing as a
journey, importance of faith and spirituality, overcoming relational difficulties, reframing self-
perception, and the ongoing impact of trauma. Resilience and recovery from childhood trauma
were characterized by severalOparticipants as a continuous process or journey rather than a final
destination. As Michael Blondino expressed:
"I think resilience is a reflection of the therapy of healing that God takes you through to
restore and bring well-being where you're not well in relationships. You can't trust people
you can't communicate with...it's a healing walk, and it's both transformational. It's
therapeutic; it's restorative."
This highlights the gradual nature of healing and building resilience over time.
For several participants, faith and spirituality played a crucial role in their healing
journey. Camille Osier shared how her faith helped her forgive her abuser: “I would have still
been able to say to him, I forgive you like God forgives...and he throws it in the sea of
forgetfulness...I'm just going to forgive you for what happened." This demonstrates how some of
the partipants found strength and healing through their faith in God. Some participants described
how childhood trauma impacted their ability to form healthy relationships, but healing allowed
each participant to connect with others. Mike shared, "I can connect with people now where I
couldn't. I can love people now, and where I before I was utterly broken. “This shows the
progression from isolation to connection that can occur through healing. Participants often had to
reframe how they viewed themselves as they healed. Mike shared, "I wouldn't call myself an

149
introvert anymore...that was a part of my trauma.” This illustrates how healing can lead to new
understandings of one's personality and identity.
While describing their resilience, participants also acknowledged the ongoing impact of
their trauma. As Camille Osier noted about her sexual abuse: “I can still remember the
incidences, but I don't any longer have that bitterness or that anger, because I've forgiven him."
This highlights how memories may remain even as emotional healing occurs. The essence of
these lived experiences involves a complex, ongoing journey of healing that touches on
spirituality, relationships, self-perception, and managing the long-term effects of childhood
trauma. The path to resilience is described as gradual but transformative.
RQ2: What are the perceived long-term effects of childhood trauma on the lives of adults, as
revealed through their first-hand accounts and reflections?
Participants identify several common themes concerning the long-term effects of
childhood trauma on adults, including difficulties in forming healthy relationships. Sexual and
intimacy concerns. Substance abuse, low self-esteem and negative self-perception, ongoing
emotional and psychological struggles, resilience, and post-traumatic growth. Several
participants described challenges in forming and maintaining relationships as adults due to their
childhood trauma. For example, Mike shared "I have always been an introvert because of the
damage that I experienced as a child...Being with people was stressful and caused me to be
anxious.” He went on to explain how healing allowed him to connect better with others stating "I
can connect with people now where I couldn't. I can love people now, and where I before I was
utterly broken." Cammy described how her childhood sexual abuse impacted her ability to enjoy
intimacy as an adult. She stated, "I didn't really recognize that I still had some real sexual issues

150
until after I became a Christian...that was the thing about not being able to relax and enjoy being
with my husband."
Several participants mentioned using drugs or alcohol to cope with their trauma. David
stated, "I was involved in a lot of drug abuse and stuff like that...I was very much a hurting kid
for sure." The trauma impacted how participants viewed themselves. According to Tachianna,
"You're overanalyzing everything you do. You want to know more about your relationship with
God. Everything hurts you when you look at it. Many said they were still dealing with the
emotional effects of their stress as adults. Penny stated "I can still remember the incidences, but I
don't any longer have that bitterness or that anger, because I've forgiven him." Even though there
were some bad effects, many of the participants said they became more resilient and grew in
good ways. "It's a healing walk, and it's also a transformational walk," Mike said. It heals and
restores in a way. These themes show how childhood tragedy can have complicated and long-
lasting effects, but also how people can heal and grow over time. The first-person accounts give
us a lot of information about how people think about and remember the effects of traumatic
events that happened to them as children.
RQ3: How do adults who experienced childhood trauma describe how their experiences have
shaped their understanding of themselves and their world?
All Every participant shared insights into how their childhood trauma profoundly
influenced their self-perception. For example, Michael Blondino described how he identified as
an introvert as a result of his trauma. He shared, "I have always been an introvert because of the
damage that I experienced as a child... I wouldn't call myself an introvert anymore... that was a
part of my trauma." Participants frequently mentioned challenges in forming and maintaining
relationships as a result of their trauma. Mike shared, "I can connect with people now where I

151
couldn't. I can love people now, and where I was before I was utterly broken." Camille also
described difficulties in her marital relationship due to her childhood sexual abuse. She stated, "I
didn't really recognize that I still had some real sexual issues until after I became a
Christian...that was the thing about not being able to relax and enjoy being with my husband."
The participants who experienced sexual abuse had their understanding of sexuality
significantly affected by their trauma. Camille shared, “When you're sexually abused like that
very young. It also makes you very sexually curious... but I never enjoyed myself even with that
when I was experimenting with sex at a young age.” Despite the negative impacts, many
participants described how overcoming their trauma led to personal growth and resilience. David
stated, “It’s a healing walk, and it's both transformational. It's therapeutic; it's restorative."
Several participants described how their faith played a crucial role in their healing process and
shaped their worldview. Camille shared, "until I was able to let God heal me from and
reinterpreted what a healthy, loving, sexual relationship was all about, and what it meant... it
wasn't until then that I was able to actually relax and enjoy being with my husband that way."
Participants described healing from trauma as an ongoing journey rather than a destination. Alex
shared, "I think resilience is a reflection of the therapy of healing that God takes you through to
restore and bring well-being where you're not well in relationships.”
In summary, adults who experienced childhood trauma describe their experiences as
profoundly shaping their self-perception, relationships, sexuality, spirituality, and overall
worldview. While the impacts were often negative initially, many found ways to grow, heal, and
develop resilience through their journey of recovery.

152
Summary
The results of the study following theme analysis were presented in this chapter. The
findings were analyzed in relation to the theme development and responses to the research
questions. Narrative profiles with synopses of the participants' backgrounds were used to
introduce them. TheOthree themes that emerged from the data are faith in God and His
transformative work, support from others, and having a sense of purpose or calling. These
themes represent the core elements that participants identified as crucial in their journey towards
resilience. The theme of faith in God highlights the importance of spiritual beliefs and practices
in helping individuals cope with and overcome adverse experiences. Support from others
emerged as a critical factor, emphasizing the role of relationships and social connections in
fostering resilience. The third theme, having a sense of purpose or calling, underscores the
significance of finding meaning and direction in life as a means of overcoming adversity.
The participants' lived experiences demonstrated their perceptions of how resiliency
influenced their Adverse Childhood Experiences (ACEs). The study examined the distinction
between individuals who have developed as well as the influence of each participant's personal
definitions of resilience. The results indicated that how individuals conceptualized resilience
often shaped their approach to challenges and their perception of their own ability to overcome
adversity. These personal definitions ranged from seeing resilience as the ability to bounce back
from setbacks to viewing it as a process of continuous growth and adaptation. This chapter's
findings provide an in-depth understandingOof resilience concerning Adverse Childhood
Experiences. This study offers valuable insights into trauma and resilience research by
presenting themes derived from the data, analyzing participants' lived experiences, and
examining the influence of personal definitions of resilience. The findings offer important

“reo
153
implications for the development of interventions and support systems for individuals who have
encountered childhood adversity.

154
Chapter Five: Conclusion
Overview
In this qualitative phenomenological study, I explored the lives of individuals in the
Pacific Northwest who have overcome adverse childhood experiences and have demonstrated
resiliency in adulthood. My research offers those intrigued in resolving Adverse Childhood
Experiences (ACEs) and fostering resilience with empirical evidence directly obtained from
resilient individuals. The research participants provided valuable insights into the protective
elements that enhanced their resilience, as well as the challenges and systemic obstacles they
encountered. The study findings identified several themes derived from the sample population,
namely: (1)Ogiving back, (2) religious beliefs and spirituality, (3) impact of unfamiliar
individuals, (4) self-compassion, (5) institutional resources as obstacles, (6) restricted access to
resources for participants from diverse racial backgrounds, and (7) generational influences.
The findings of the study are reviewed and explained in this chapter. It evaluates the
extent to which these correspond with the theoretical frameworks and the existing literature that
served as the foundation for the investigative process. The chapter will also examine procedure
limitations that could affect the findings' applicability and generalizability. The implications of
the outcome and potential avenues for further investigation will be addressed. The chapter will
conclude with a concise summary of the study's fundamental significance and its applicability to
the broader community, theory, and practice.
Summary of Findings
This section presents an overview of the research findings pertaining to the themes that
emerged from the data and the study's research questions. The research employed a qualitative
approach to hermeneutical phenomenology, as described by Miles et al. (2020), to explore the

155
lived experiences of the participants. The analysis of data from 8 interviews yielded three main
themes. These themes represent the common threads that ran through the participants' narratives,
providing insight into their shared experiences and perspectives. The use of hermeneutical
phenomenology allowed for a deep exploration of these themes, focusing on the interpretation of
the participants' lived experiences and the meanings they ascribed to them. The emergence of
these themes from the interview data underscores the value of qualitative research in capturing
the nuanced and complex nature of human experiences. By allowing participants to share their
stories in their own words, the study was able to uncover rich, detailed insights that might not
have been accessible through quantitative methods alone. These themes serve as a framework for
understanding the participants' experiences and provide a foundation for addressing the study's
research questions. In the following sections, each of these themes will be explored in detail,
supported by relevant quotes from the participants and connections to existing literature. This
analysis will provide a comprehensive understanding of the findings and their implications for
the field of study.
Themes
Themes were developed during the interview process and then refined while reviewing
the transcripts. In the process of conducting interviews and subsequently examining transcripts, I
began to identify commonalities and distinctions in the attitudes and beliefs of the participants
regarding resilience, as well as their personal experiences with it, and the ability to develop
resilience and the internalized definition of resilience. After going over the transcripts, I found
the commonalities and established three main themes that participants have in common. Three
themes were kept because they were clear and consistent from the start of the study. Three
themes became apparent when the data from the ten interviews was analyzed. The three main

156
themes are faith in God and His transformative power, support from others, and having a sense
of purpose or calling. Although all participants shared common themes, their level of comfort
with and capacity for defining resilience varied, making it necessary to classify them based on
how they connected to the identified themes.
Research Questions
The narratives provided by the participants effectively addressed each of the research
questions posed in this study. These personal accounts offered rich, detailed insights that directly
contributed to our understanding of the phenomena under investigation. The participants' stories
provided nuanced perspectives on their experiences, shedding light on the complex interplay of
factors related to the research questions. By sharing their lived experiences, the participants
offered valuable context and depth to the study's inquiries, allowing for a more comprehensive
exploration of the topics at hand. The alignment between the participants' narratives and the
research questions underscores the effectiveness of the chosen methodology in eliciting relevant
and meaningful data. This congruence between the research questions and the collected data
strengthens the validity of the study's findings and provides a solid foundation for further
analysis and interpretation.
RQ1: How do adults who experienced childhood trauma describe the essence of their lived
experiences?
According to several interviewees, their childhood trauma was a severely upsetting and
harmful event that destroyed their feeling of security, self-worth, and trust. Dale describes being
severely sexually abused beginning when he was eleven years old, which caused him to feel
alone, uncertain of who he was, and afraid. Tachianna talks about how her adoptive parents
mistreated her physically and emotionally, making her feel unloved and unworthy. Because of

157
her horrible experiences, Patsy talks about feeling suicidal and wishing she had never been born.
Many participants highlighted their natural resilience and will to live despite the severe scars
caused by their tragedy. Dale talks about how his innate self-assurance and daring nature enabled
him to recover. He continues, "I just knew that I'd gone through a lot of hits, and I still got back
up, and I was still standing." According to Patsy, she refused to qive up because "I didn't know
giving up was an option." They frequently had a feeling of purpose or calling that provided them
motivation to keep going, which strengthened their inner strength. All interviewees seek finding
healing and making meaning of their experiences which depended heavily on their faith and
spirituality. The ability to "hear God's voice even when it was the darkest" is what Dale says
gave him hope. According to Mike, his recovery process is an example of "the therapy of healing
that God takes you through to restore and bring well-being."
It was said that the change and healing process was slow and continuous. Many
mentioned that they needed to actively work on their rehabilitation, frequently with the help of
faith communities, therapists, or caring mentors. Mike describes how his recovery helped him
change from a reclusive recluse to a person who can truly love and connect with others.
Although extremely unpleasant, a number of participants highlighted how their traumatic
experiences eventually molded them in ways that enabled them to assist others. They talked of
being more resilient, empathetic, and driven to use their experiences to change the world. David
shared, “I just know that somewhere down my path, this is gonna make sense.”
RQ2: What are the perceived long-term effects of childhood trauma on the lives of adults, as
revealed through their first-hand accounts and reflections?
Participants who have taken part in forgiveness report that it plays a significant role in the
resilience process. Some of the participants mentioned that forgiveness was extremely crucial for

158
their resilience and helped them start to become truly resilient. Some other participants
mentioned that forgiveness came from their journey of resilience and served as proof of how
they had progressed in their resilience.OParticipants who haven't engaged in forgiveness see their
struggle to do so as a hurdle to building resilience. This shows that they understand forgiveness
could make their experience better, but they struggle to actually forgive and become resilient.
RQ3: How do adults who experienced childhood trauma describe how their experiences have
shaped their understanding of themselves and their world?
All participants initially struggled with low self-esteem, confusion about their identity,
and difficulty trusting others as a result of their trauma. They often felt isolated, different from
peers, and unsure of their place in the world. Several described feeling-like victims and
questioning why they had to endure such difficult experiences at a young age. However, as they
worked through healing processes, many came to view their traumatic experiences as sources of
strength and resilience. They developed a deeper sense of empathy, compassion, and desire to
help others who have experienced similar trauma. Several mentioned that their faith and
spirituality played a key role in reframing their experiences and finding meaning. Several
participants described how overcoming trauma gave them a sense of inner strength and the
confidence that they could face future challenges. They came to see themselves as survivors
rather than victims. Some participants mentioned developing a strong drive to set and achieve
goals as a way of proving to themselves that their past did not define them. Their worldview was
often shaped by a heightened awareness of human suffering and injustice, but also by a belief in
the human capacity for healing and growth. Many expressed a commitment to breaking cycles of
abuse and creating positive change. Overall, while the trauma had lasting impacts, many

159
ultimately integrated these experiences into a more complex, resilient sense of self and
worldview focused on growth and helping others.
Discussion
This section aims to correlate the findings of the current study with the empirical and
theoretical results of prior research discussed in Chapter Two's literature review. The narratives
shared by the participants vividly illustrate the adverse effects and challenges documented in the
literature that are prevalent among individuals who have endured Adverse Childhood
Experiences (ACEs). The participants' real-life experiences closely align with the outcomes
outlined in the existing body of research, providing a rich, qualitative validation of previous
findings. This congruence between the study's results and established literature strengthens the
validity of both the current research and the broader understanding of ACEs' impacts. By
examining these correlations, we can gain deeper insight into the long-term effects of childhood
adversity and the processes of resilience development. The subsequent subsections will delve
into specific areas of the literature, exploring how the participants' experiences reflect, expand
upon, or potentially challenge existing knowledge in the field.
Connection to Current Literature
The experiences of the participants areOconsistent with the current body of research on the
long-term effects of adverse childhood experiences (ACEs) and the process of establishing
resilience. Several individuals, for instance, expressed continued challenges with relationships,
self-esteem, and mental health issues far into adulthood. This finding is in line with the seminal
ACE study conducted by Felitti et al. (1998), which discovered a high association between
childhood trauma and adult health outcomes.

160
The findings of Werner and Smith's (1992) longitudinal study on resilience, which
highlighted caring relationships as a crucial protective factor for at-risk children, are supported
by the fact that many participants underlined the significance of supporting relationships in the
process of creating resilience. Underscoring the significance of social support in the process of
resilience is the fact that this is the case. More recent research continues to support these
connections. The new study provides substantial support for the findings of Werner and Smith's
(1992) longitudinal study on resilience, which identified caring connections as a critical
protective element for children at risk. The importance of social support in this process was
highlighted by the several study participants who stressed the vital role that supportive
connections play in building resilience. The connection with Werner and Smith's groundbreaking
research highlights the lasting value of social ties in fostering resilience, especially for people
who are experiencing hardship. According to the Kauai Longitudinal Study, which tracked
participants from infancy to adulthood, resilient kids frequently had at least one supportive adult
in their lives. In a similar vein, survey participants regularly mentioned the presence of
supporting individuals as being crucial to their capacity to overcome obstacles and grow
resilient. Furthermore, it appears that a key factor in building resilience is the kind of social
support one receives. Resilience has been repeatedly associated with emotional support, which
gives people a feeling of being cared for and appreciated. This supports the findings of Werner
and Smith, who noted that connections between resilient kids were frequently marked by warmth
and emotional openness.
The new research on resilience by Werner and Smith is firmly supported by the existing
findings. Social ties are crucial for building resilience, especially for people who are enduring
adversity, as evidenced by the constant emphasis on supporting relationships as a major

161
protective element. This long-standing relationship between resilience and social support offers
important information for creating interventions and support networks that effectively assist
people in overcoming obstacles and thriving in the face of hardship (Bellis et al., 2018).
Many participants emphasized the critical role of supportive relationships in building
resilience, which aligns with Werner and Smith's landmark longitudinal study on resilience.
Their research highlighted caring relationships as a key protective factor for at-risk children. This
finding has been consistently reinforced by recent studies, further solidifying the importance of
social support in fostering resilience. A 2024 study provided compelling evidence for the
significance of social support and resilience in mental health outcomes (Moisoglou et al., 2024).
The research found that these factors were significantly associated with reduced anxiety and
depression, as well as improved quality of life among individuals with post-COVID syndrome.
This underscores the enduring relevance of supportive relationships in promoting resilience, even
in the face of contemporary health challenges. Furthermore, research focusing on pregnant
patients has shed light on the interplay between adverse childhood experiences (ACEs),
resilience, and mental health (Shaffer, 2024). The study revealed that both ACEs and low
resilience were linked to higher odds of developing depression or anxiety during pregnancy.
These findings not only highlight the ongoing impact of childhood adversity into adulthood but
also emphasize the protective role that resilience can play in mitigating these effects. This
research underscores the importance of fostering resilience as a means of promoting mental
health, particularly for individuals with a history of childhood adversity.
The participants' narratives reflect the understanding of resilience as a dynamic process
rather than a fixed trait. This perspective aligns with current resilience research, particularly the
work of Ann Masten, which emphasizes that resilience emerges from ordinary processes and

162
adaptive systems (WestEd, 2004). This conceptualization of resilience as a malleable quality that
can be developed over time has significant implications for intervention and support strategies.
The varied paths to resilience described by participants support the idea that resilience can be
cultivated through multiple avenues. One such avenue is community involvement and social
connections. Engaging with one's community and building a network of social support can
provide individuals with resources, emotional sustenance, and a sense of belonging, all of which
contribute to enhanced resilience (Bellis et al., 2018).
Access to supportive adults and role models during childhood is another crucial pathway
to resilience. These relationships can offer guidance, emotional support, and positive examples,
helping children navigate adversity and develop adaptive coping strategies (Bellis et al., 2018).
The presence of at least one caring adult can make a significant difference in a child's ability to
overcome challenges and build resilience (Cao et al., 2024). Opportunities to develop coping
skills and self-efficacy also play a vital role in fostering resilience. By learning and practicing
effective coping mechanisms, individuals can better manage stress and adversity. Moreover,
building self-efficacy, the belief in one's ability to handle challenges, can significantly enhance
resilience, as it empowers individuals to face difficulties with confidence and perseverance (Cao
et al., 2024). These findings underscore the multifaceted nature of resilience development and
highlight potential areas for intervention and support. By focusing on these various pathways,
practitioners and policymakers can design more comprehensive and effective strategies to
promote resilience across diverse populations and contexts.
Extension to Previous Research
This study not only validates much of the current literature but also enhances our
comprehension in several important areas:

163
Resilience as a Continuous Process
Participants frequently characterized resilience as a dynamic, continuous process of
development and recovery rather than as a fixed trait. The view of resilience as a developmental
process introduced by Luthar et al. (2000) and Masten (2001) is aligned with this, and it further
expands the concept of resilience. The view of resilience as a developmental process, first
proposed by Luthar et al. (2000), marked a significant shift in understanding this phenomenon.
Their work emphasized that resilience is not a static characteristic but rather a capacity that can
be nurtured and developed over time. This conceptualization opened up new avenues for
research and intervention, suggesting that resilience could be fostered even in individuals who
had experienced significant adversity.
Building on this foundation, Masten's (2001) influential work further refined the
understanding of resilience as a dynamic process. Masten proposed that resilience emerges from
ordinary adaptive processes, challenging the notion that resilient individuals possess
extraordinary qualities. This "ordinary magic" perspective highlighted the potential for
resilience-building interventions across diverse populations and contexts. The participants'
narratives in the current study not only support these seminal works but also contribute to the
evolving understanding of resilience. By describing their experiences of developing and
recovering resilience over time, the participants provide rich, qualitative evidence for the
dynamic nature of this construction. Their accounts underscore the potential for growth and
adaptation even in the face of ongoing challenges, reinforcing the importance of viewing
resilience as a continuous process rather than a fixed outcome. This alignment between
participant experiences and established theoretical frameworks strengthens the validity of both
the current study's findings and the broader conceptualization of resilience in the field. It also

164
highlights the potential for interventions that support the ongoing development of resilience
throughout the lifespan, rather than focusing solely on early childhood or crisis periods.
Research and practice will be significantly impacted by the idea that resilience is a
continual process (Masten, 2001). This understanding calls for long-term studies that can
document resilience's rise and fall across time. The elements that contribute to resilience
development at different times of life and the possibility that resilience may be enhanced or
weakened in response to diverse life situations can both be shown by such studies (Masten,
2001). The rising understanding in developmental psychology of the value of examining
trajectories rather than static outcomes is consistent with this methodology. In terms of practical
applications, viewing resilience as a continuous process opens up new possibilities for
intervention and support. It suggests that there are multiple points of entry for fostering
resilience, from early childhood through to late adulthood (Masten, 2001). This perspective
encourages the development of age-appropriate interventions that can bolster resilience at
different life stages. For example, programs for adolescents might focus on building self-efficacy
and problem-solving skills, while interventions for adults might emphasize stress management
techniques and the cultivation of supportive social networks. Moreover, this understanding of
resilience as a dynamic process underscores the importance of creating environments that
continually support and nurture resilience, rather than relying on one-time interventions. This
could involve developing policies and practices in schools, workplaces, and communities that
actively promote factors known to enhance resilience, such as social connectedness,
opportunities for meaningful participation, and access to resources.

165
Spiritual Aspects of Resilience
The spiritual dimensions of resilience were highlighted by numerous participants, who
underscored the significance of faith and spirituality in their resilience journeys. This adds depth
to the findings of Pargament and Cummings (2010) regarding religious coping mechanisms. This
study offers detailed personal accounts that demonstrate how spiritual beliefs can act as a source
of resilience and significance when confronting trauma. Participants' accounts revealed that
spirituality serves as a vital component of resilience, leading to subjective well-being and
accumulating resilience over the course of life. For many, spiritual resilience acted as a tool
aiding recovery from adversity, sustaining a sense of well-being, and fostering spiritual and
developmental growth as they aged. This aligns with the concept of spiritual resilience as the
ability to maintain one's sense of self and purpose through beliefs, principles, or values while
encountering adversity, stress, and trauma.
The study identified five key domains of spiritual resilience: relationships rooted in
spirituality, a belief structure and complementary worldview, spiritual coping, commitment to
spiritual values and practices, and openness to spiritual growth and transformation. Participants
frequently described relying on relationships within their spiritual community or with a divine
support system as crucial in navigating hardship. This spiritual support network provided a
framework for guiding individuals through life's challenges and facilitated positive outcomes
from negative experiences. Furthermore, the research highlighted the complex interplay between
spirituality and resilience. For many participants, spirituality provided a source of comfort,
meaning, and purpose in the face of adversity. It offered a pathway to resilience that ultimately
led to subjective well-being and spiritual growth. This finding supports previous research

166
suggesting that spirituality can serve as a factor guiding people through life challenges and
functioning as a pathway to resilience and maintaining well-being.
Themes from the study indicated that the relationship between spirituality and resilience
has a beneficial effect on mental health and overall well-being. Research has demonstrated that
people who incorporate spirituality into their coping strategies frequently have reduced levels of
anxiety and despair and higher levels of happiness with their lives. There are a number of
reasons that could explain the protective effect of spiritual resilience. These include the social
support that is frequently found in spiritual communities, the sense of meaning and purpose that
comes from spiritual beliefs, and the practice of mindfulness or meditation that is associated with
many spiritual traditions. Furthermore, spirituality can help reduce stress by providing a wider
perspective on the challenges of life and encouraging a sense of acceptance or surrender to
situations that are beyond one's control. As research in this field continues to develop, there is an
increasing awareness of the possible advantages of including spiritual components in treatments
for mental health and therapies that help build resilience.
Reframing Trauma Experiences
Participants frequently articulated a transformation in their viewpoint or a
recontextualization of their traumatic experiences as an integral component of their healing
journey. This cognitive reappraisal corresponds with the work of Folkman and Moskowitz
(2000) on positive reappraisal as a coping strategy, while also expanding on it by offering
detailed insights into how this process develops in the context of childhood trauma. Expanding
on Folkman and Moskowitz's work, the present study offers detailed insights into how this
reappraisal process develops specifically in the context of childhood trauma. Participants
described not only finding positive aspects in their experiences but also using their reframed

167
narratives to break free from cycles of victimhood. This aligns with research suggesting that
situating traumatic experiences within a broader life narrative can lead to post-traumatic growth.
The reframing process described by participants also incorporates elements of what Bonetti
terms "cognitive reappraisal" in trauma recovery. This involves reinterpreting stressful or
emotionally charged situations to alter their emotional impact, reducing the intensity of negative
emotions and promoting adaptive coping strategies. By reframing their childhood trauma,
participants reported enhanced emotional regulation and increased resilience in the face of
ongoing challenges.
Furthermore, the study's findings highlight the importance of combining reappraisal with
other strategies, such as self-distancing and acceptance. Research has shown that when negative
experiences are highly emotionally intense, reflecting from a distanced perspective can enhance
coherence and existential mattering more effectively than positive reappraisal alone. This multi-
faceted approach to reframing trauma experiences underscores the complexity of the healing
process and the need for tailored interventions in trauma recovery. The combination of cognitive
reappraisal and self-distancing methods in trauma recovery corresponds with recent
neuroimaging research that discusses the neural mechanisms involved in these processes. Studies
indicate that individuals who consistently employ cognitive reappraisal exhibit enhanced down-
regulation of amygdala activation during guided emotion regulation, including those with
remitted depression. This indicates that consistent engagement in reappraisal may enhance the
efficiency of emotion regulation at the neural level. Research indicates that self-distancing
correlates with diminished amygdala activation during the processing of traumatic memories,
which may lead to lower emotional reactivity. The findings establish a neurobiological

168
foundation for the efficacy of implementing reappraisal and self-distancing strategies in trauma
recovery.
The study's results highlight the dynamic nature of trauma recovery and the significance
of promoting psychological flexibility. The capacity to transition among various coping
strategies, including reappraisal, acceptance, and self-distancing, is essential for effective
functioning when confronted with trauma-related difficulties. The flexibility mindset enables
individuals to customize their strategies according to particular circumstances and emotional
intensities, which may result in more effective long-term outcomes. Future research may
investigate optimal methods for fostering psychological flexibility in trauma survivors,
potentially through interventions that explicitly instruct and practice various emotion regulation
strategies. This approach may improve resilience and facilitate post-traumatic growth by
providing individuals with a variety of coping mechanisms to manage the complexities of trauma
recovery.
Extension of Theoretical Framework
This study presents several significant theoretical advancements in the area of resilience,
especially concerning adults who have faced childhood trauma. The results indicate a
comprehensive model of resilience that includes biological, psychological, social, and spiritual
aspects. This comprehensive approach enhances current theories by highlighting the
interrelatedness of these components in the resilience process. For instance, Mike characterizes
resilience as "a manifestation of the healing process that God guides you through to restore and
enhance well-being in areas where relationships may be lacking." This viewpoint is consistent
with and expands upon Masten's (2001) understanding of resilience as a dynamic process while
incorporating a spiritual aspect that is frequently neglected in conventional frameworks. The

169
investigation emphasizes the distinctive elements of resilience formation in relation to childhood
trauma, indicating the necessity for a trauma-informed perspective on resilience theory. This
builds upon the findings of Luthar et al. (2000) regarding resilience as a developmental process,
focusing on the challenges and growth opportunities linked to early adversity. For example,
Alex's account of his journey from trauma to resilience demonstrates how the experience of
overcoming childhood abuse can influence one's perception of resilience and personal
development.
The narratives of participants illustrate how resilience evolves throughout different life
stages, spanning from childhood to adulthood. This temporal perspective enhances current
models of resilience, indicating the necessity for life-course approaches that take into account the
evolution of resilience throughout various developmental stages. Dale's narrative of his journey
through resilience, beginning with childhood trauma and evolving into adult ministry, illustrates
a comprehensive view on the development of resilience over time. The study offers detailed,
personal accounts that demonstrate how spiritual beliefs can act as a source of resilience and
significance when confronting trauma. This expands on the findings of Pargament and
Cummings (2010) regarding religious coping mechanisms, providing in-depth analyses of how
faith enhances resilience in situations of childhood trauma. Camille Osier's account of how her
beliefs facilitated her forgiveness for her abuser and contributed to her healing from sexual
trauma serves as a compelling illustration of the spiritual aspect of resilience.
Participants frequently articulated a transformation in their viewpoint or a recontextualization of
their traumatic experiences as an integral component of their healing journey. This cognitive
reappraisal corresponds with the work of Folkman and Moskowitz (2000) on positive reappraisal
as a coping strategy, while also expanding on it by offering comprehensive insights into how this

170
process develops in the context of childhood trauma. Mike’s reinterpretation of his introversion
as a response to trauma, rather than a fixed personality characteristic, exemplifies this process.
In summary, this study validates and builds upon earlier findings regarding resilience in
adults who have faced childhood trauma. Through detailed, firsthand narratives of the resilience
process, it presents important insights that can enhance both theoretical understanding and
practical application in this area. The results emphasize the intricate and varied aspects of
resilience, showcasing the necessity of taking into account personal experiences and contexts to
comprehend and promote resilience effectively.
Implications
This study found results that are important for theory, research, and real-world
applications. The implications relate to earlier studies and highlight problems that can be fixed
and policies that should be improved, enhanced, or created. The findings contribute to the current
research on the phenomena being studied and show a clear link to earlier studies on Adverse
Childhood Experiences and Resilience theory. This section addresses these implications.
Theoretical
The findings from the data collected in this study correspond with the theoretical
framework that supports this research. The lived experiences of the participants in this study
exemplified the Resilience Theory. Individuals lacking fundamental connection, validation, and
safety from the adults responsible for their upbringing cultivated self-perceptions that were, at
best, misguided and often profoundly harmful to their identity formation and self-esteem
development. The interviews demonstrate that resilience is a dynamic process that evolves over
time rather than a fixed attribute. This is consistent with the current perspective of resilience
theory, which regards resilience as a capacity that can be developed and reinforced, rather than

171
an inherent trait. Chen et al.'s research from 2024 supports this, demonstrating that resilience can
mitigate and reduce the association between adverse outcomes and early trauma. This implies
that resilience is dynamic and can be cultivated as a means of protection.
The experiences of the individuals demonstrate the complexity of resilience, which
includes social, psychological, and spiritual components. This illustrates the focus of resilience
theory on analyzing protective factors at various levels: individual, relational, and contextual.
According to Masten (2018), the ecological perspective articulated in the Child Trends report
further substantiates the understanding of resilience through this multifaceted framework. A
recurring motif was the essential function of supportive relationships in cultivating resilience.
This is closely aligned with the principles of resilience theory, which emphasizes the significance
of supportive relationships as a crucial protective factor, particularly for children who have
experienced trauma. The Child Trends report highlights that the most significant protective
factor associated with resilience in the face of childhood trauma is the consistent presence of a
sensitive, nurturing, and responsive adult.
The stories of the subjects show how positive adaptation can happen in the face of major
hardship. This is what resilience theory is all about. It's important to look at strengths and good
outcomes, not just psychopathology or the bad effects of trauma, according to resilience theory.
These theoretical results show how complicated and changing resilience is and how important it
is to look at a lot of different factors and levels of influence when studying and building
resilience, especially when it comes to childhood trauma.
Empirical
The empirical implications of resilience theory, as collected from the participants'
interviews, offer a sophisticated insight into the ways individuals adapt and flourish in the face of

172
Adverse Childhood Experiences. The interviews highlight several fundamental elements of
resilience theory that possess significant implications for both academic inquiry and therapeutic
practices. Resilience is emphasized as a fluid process rather than a static characteristic. The
narratives of participants illustrate that resilience is cultivated progressively through a multitude
of experiences and interventions. This is consistent with the principles of resilience theory,
which suggest that resilience may be developed and enhanced through nurturing relationships,
individual development, and effective coping strategies. The interviews indicate that resilience is
not merely an innate trait but rather a capacity that can be cultivated, providing optimism for
interventions that aim to strengthen resilience in individuals who have faced trauma.
The interviews highlight the complex and multifaceted characteristics of resilience.
Participants talked about using spiritual, social, and psychological resources to help them deal
with their difficulties. There are different levels of influence that can help people be resilient,
such as the person, the relationship, and the situation. This supports the ecological perspective in
resilience theory. The existence of supportive relationships, including mentors and community
members, proved essential for numerous participants, emphasizing the theory that external social
support serves as a vital protective aspect to the cultivation of resilience. Furthermore, the notion
of steeling effects,Owhich refers to the constructive development that arises from facing
challenges, is clearly illustrated in the narratives of the participants. A number of individuals
articulated how overcoming their traumatic experiences promoted a heightened sense of
resilience and an aspiration towards helping others. This corresponds with elements of resilience
theory that emphasize post-traumatic growth and the capacity for adversity to cultivate enhanced
resilience under specific circumstances.

173
Lastly, the interviews emphasize how critical cognitive reframing and meanin-making are
to the resilience process. Participants frequently discovered ways to view their experiences in a
more positive light or find meaning in their struggles, aligning with theoretical models that
highlight the role of cognitive processes in resilience. This implies that treatment modalities that
assist people in reframing their stories and discovering significance in their experiences may be
more successful in cultivating resilience. Overall, by showing how theoretical ideas appear in
actual situations, these empirical insights from the interviews deepen our knowledge of resilience
theory. They demonstrate possible avenues for assisting those who have suffered from childhood
trauma and stress the significance of considering resilience as a multifaceted, dynamic process
impacted by a variety of circumstances.
Implications for Practice
Several key implications for practice have emerged from this study’s findings.
Fostering Supportive Relationships
The crucial role that supportive relationships play in building resilience was a recurring
subject in all of the interviews. When working with people who have suffered trauma,
practitioners should concentrate on assisting them in establishing and preserving healthy,
supportive relationships. Connecting clients with community organizations that may offer
continuous social support, mentoring programs, or support groups may be one way to do this.
Supportive relationships serve as a cornerstone for resilience in trauma recovery. These
connections provide individuals with a sense of safety, understanding, and validation that is often
lacking in the aftermath of traumatic experiences. By fostering such relationships, practitioners
can help trauma survivors rebuild their sense of trust and security in the world around them.

174
These supportive bonds act as a buffer against the negative effects of trauma, offering emotional
sustenance and practical assistance during the healing process.
Furthermore, the efficacy of therapeutic interventions can be considerably increased by
supportive relationships. By encouraging healthy coping mechanisms and offering support
during trying times, they establish a network of care that goes beyond the professional setting.
Peer support groups, friendships, family ties, and professional mentoring are just a few examples
of the different ways these interactions can manifest. From the unconditional affection of family
to the shared experiences in support groups, each kind of connection has its own advantages. In
addition to assisting in the development of new supportive connections, practitioners should seek
to identify and fortify any already-existing ones in their clients' lives.
Partnerships and quality are just as significant as existence. Positive communication,
empathy, and mutual respect are traits of strong, sustaining relationships. They give trauma
survivors a place where they may express themselves without worrying about criticism or
rejection. Practitioners can be quite helpful in assisting clients in acquiring the abilities required
to establish and preserve these kinds of relationships, such as effective communication, creating
boundaries, and handling conflict. Post-traumatic growth, a phenomenon in which people
undergo beneficial psychological changes as a result of their battle with trauma, can be
facilitated by supportive connections. Through these connections, survivors can gain a deeper
understanding of life, uncover personal talents they may not have previously acknowledged, and
find new meaning in their experiences. Supportive people who offer perspective, encouragement,
and hope for the future can help to foster this progress.

175
Promoting a Sense of Purpose
Several participants shared how feeling a sense of purpose or calling supported them in
overcoming challenges. This finding underscores the importance of purpose as a powerful
motivator and source of resilience in the face of adversity.A sense of purpose provides
individuals with a clear direction and a compelling reason to persevere through difficulties. It
acts as an internal compass, guiding decisions and actions towards meaningful goals. For many
participants, this sense of purpose served as a beacon of hope during their darkest moments,
providing the strength and motivation needed to push forward. The concept of purpose extends
beyond mere goal setting; it encompasses a deeper understanding of one's values, passions, and
place in the world. Participants who reported a strong sense of purpose often described feelings
connected to something larger than themselves, whether through their work, relationships, or
personal aspirations. This connection to a greater cause or meaning appeared to bolster their
resilience and determination.
For practitioners working with individuals facing challenges, it is crucial to collaborate
with clients in identifying and developing purposeful goals. This process involves a thorough
exploration of personal values, interests, and strengths. By helping clients uncover what truly
matters to them, practitioners can assist in cultivating a sense of direction and intrinsic
motivation. The process of finding purpose is highly individualized and may involve various
approaches. Some effective strategies include engaging in self-reflection exercises, exploring
past experiences for patterns of fulfillment, and identifying core values. Practitioners can guide
clients through these exercises, helping them articulate their deepest aspirations and translating
them into actionable goals.

176
Additionally, encouraging clients to explore new activities or revisit forgotten passions
can be instrumental in uncovering sources of purpose. Engaging in volunteer work, pursuing
further education, or exploring career changes are potential avenues for discovering meaningful
pursuits that align with one's values and strengths. It’s important to note that a sense of purpose
may evolve over time. Practitioners should emphasize the dynamic nature of purpose and
encourage clients to regularly reassess and refine their goals as they grow and change. This
flexibility allows individuals to adapt their sense of purpose to new circumstances and
challenges, maintaining its relevance and motivational power. By focusing on promoting a sense
of purpose, practitioners can empower clients with a powerful tool for overcoming challenges
and building long-term resilience. A strong sense of purpose not only helps individuals navigate
current difficulties but also provides a foundation for continued growth and fulfillment in the
future.
Developing Coping Skills
Resilience theory emphasizes the crucial role of adaptive coping strategies in building
and maintaining resilience. Practitioners working to enhance their clients' resilience should focus
on helping them develop a comprehensive toolkit of effective coping mechanisms. One key
aspect of this toolkit is mindfulness techniques. Mindfulness practices can help clients become
more aware of their thoughts and emotions, allowing them to respond to stressors more
effectively. Research has shown that mindfulness training can improve coping styles, reduce test
anxiety, and increase happiness in students (Zandi et al., 2021).OThese practices can enhance
emotional regulation and overall well-being, enabling individuals to navigate challenges more
successfully. Problem-solving skills are another essential component of resilience-building. By
teaching clients how to approach challenges systematically and creatively, practitioners can help

177
them feel more empowered and capable of overcoming obstacles. This aligns with the concept of
problem-focused coping, which involves tackling issues directly to reduce or eliminate stressors
(Zandi et al., 2021).ODeveloping these skills can lead to more adaptive and effective responses to
life's challenges.
Stress management strategies are also crucial for developing resilience. These can include
techniques such as deep breathing exercises, progressive muscle relaxation, or time management
skills. By equipping clients with these tools, practitioners can help them cope better with daily
stressors and more significant life challenges. Adaptive coping strategies have been shown to
improve levels of functioning and deal directly with root problems, decreasing actual stress
levels (Zandi et al., 2021). Another important aspect of building resilience is helping clients find
meaning in adversity. This aligns with the concept of appraisal-focused coping, which involves
attempting to understand and find a pattern of meaning in a crisis (Zandi et al., 2021).
Practitioners can guide clients in reflecting on challenging circumstances and
reconnecting with personal values, helping them discover meaning even in difficult situations.
Reframing adverse circumstances is a powerful cognitive strategy that can significantly enhance
resilience. This involves helping clients identify and challenge negative thought patterns,
replacing them with more balanced and constructive perspectives. Cognitive Behavioral Therapy
(CBT) techniques can be particularly effective in this regard, helping clients reframe negative
thoughts and focus on solutions rather than dwelling on problems. By focusing on these various
aspects of coping skill development, practitioners can help their clients build a robust foundation
for resilience, enabling them to navigate life's challenges more effectively and maintain overall
well-being.
Addressing Trauma Holistically

178
The interviews demonstrate how trauma and resiliency are complex, multifaceted
phenomena. Psychological, physiological, social, and spiritual components of healing should all
be considered in a comprehensive manner by practitioners. This may involve collaborating with
other professionals, such as medical doctors, social workers, or spiritual advisors, to provide
comprehensive care. A holistic approach to addressing trauma involves considering all aspects of
an individual's well-being. Psychological components include cognitive and emotional processes,
while physiological aspects encompass the body's responses to trauma. Social factors involve
relationships and support systems, and spiritual elements may include finding meaning and
purpose. This multidimensional view is supported by research showing that resilience emerges
from the interplay of individual, social, cultural, and environmental factors (Matheson et al.,
2020).
To provide comprehensive care, practitioners should collaborate with a diverse team of
professionals, which aligns with the Collaborative Care Model, which has been shown to
improve patient outcomes, save money, and reduce stigma related to mental health (Matheson et
al., 2020b).OThe model involves a team led by a primary care provider and includes behavioral
health care managers, psychiatrists, and other mental health professionals. A collaborative
approach ensures that all aspects of a patient's health are addressed, from physical to mental
well-being (Matheson et al., 2020b). Incorporating various therapeutic approaches can enhance
the effectiveness of trauma treatment. For instance, mindfulness practices, when applied in a
trauma-informed manner, have been developed to help individuals with PTSD and chronic pain
enhance their physical and psychosocial well-being by building resilience.OBody-centered
therapies, such as somatic experiencing and trauma-informed yoga, focus on processing the
residue of traumatic experiences to release them from the body and lessen triggers (Matheson et

179
al., 2020b).
Promoting Post-Traumatic Growth
Resilience theory recognizes that adversity can sometimes lead to positive personal
growth, a phenomenon known as post-traumatic growth (PTG) (Dell’Osso et al., 2022). This
concept, first introduced by Tedeschi and Calhoun in the 1990s, is defined as "positive
psychological changes experienced as a result of the struggle with trauma or highly challenging
situations" (Dell’Osso et al., 2022).OWhile acknowledging the pain and difficulty individuals
have endured, practitioners can help clients identify potential areas of growth or positive change
resulting from their experiences. Post-traumatic growth can manifest in various domains,
including improved relationships, increased personal strength, recognition of new possibilities,
spiritual development, and a greater appreciation for life (Dell’Osso et al., 2022). These changes
often emerge as individuals struggle to make sense of their traumatic experiences and reconstruct
their assumptive world views. It's important to note that PTG is not an alternative to negative
psychological consequences but rather a parallel process that can coexist with trauma-related
distress (Dell’Osso et al., 2022).
Practitioners can facilitate post-traumatic growth by implementing specific strategies in
therapy. One approach involves helping clients reframe their traumatic experiences. This
cognitive reappraisal process allows individuals to find meaning in adversity and develop a more
balanced perspective on their trauma (Dell’Osso et al., 2022).OTechniques such as narrative
therapy, where clients rewrite the ending of their traumatic story, can be particularly effective in
promoting growth and resilience (Dell’Osso et al., 2022).OAnother crucial aspect of promoting
PTG is assisting clients in developing a sense of purpose. Many individuals who experience
growth after trauma report feeling a renewed sense of meaning or calling (Dell’Osso et al.,

180
2022).OPractitioners can collaborate with clients to identify personal values, interests, and
strengths, helping them find direction and motivation in the aftermath of trauma. This process of
finding meaning can be a powerful catalyst for growth and resilience.
An essential approach of PTG promotion for practitioners involves cultural sensitivity.
Different cultures may have diverse ways of coping with trauma and conceptualizing growth
(Dell’Osso et al., 2022).OA culturally sensitive therapist recognizes and respects these
differences, avoiding the imposition of Western-centric models of trauma recovery. Such an
approach not only promotes empowerment but also prevents potential re-traumatization that
could occur by dismissing a client's cultural context. While promoting post-traumatic growth, a
crucial factor for practitioners is to maintain a delicate balance to acknowledge and validate the
client's pain and suffering while gently exploring possibilities for growth. Often referred to as
expert companionship, the intervention involves education regarding trauma responses, teaching
emotional regulation strategies, facilitating the disclosure of trauma memories, and helping
clients develop a narrative that encompasses positive aspects of the self. Incorporating strategies
and maintaining a sensitive, culturally aware approach, provides practitioners another way to
help clients navigate the complex journey from trauma to growth, fostering resilience and
promoting healing in the process (Dell’Osso et al., 2022).
Tailoring Interventions to Individual Needs
The variety of experiences revealed in the interviews emphasizes the need to customize
resilience-building treatments to every person's particular situation, cultural background, and
personal characteristics. There isn't going to be a single best way to do things. These implications
emphasize the importance of a thorough, customized strategy for developing resilience in
therapeutic settings. Practitioners can better help people in overcoming trauma and creating a

181
more resilient future by targeting several aspects of resilience and customizing solutions to each
person's particular circumstances.
One additional method to reduce ACEs and promote resilience, as established by the
results of my study, is to adopt a comprehensive and integrated healthcare strategy. This
approach involves addressing mental, physical, psychological, and spiritual health during regular
medical examinations by a team of professionals from multiple fields. Larkin et al. (2014)
advocated comprehensive treatment, and service integration will bring that to fruition by
combining medical and social science research on ACE to guide policies to help families and
individuals. Utilizing an integrated strategy allows for the proper identification and elimination
of challenges and risk factors by leveraging the resources of a multi-disciplinary team. This
healthcare service has the potential to enhance healthy coping mechanisms and protective
factors, as highlighted by participants in my study. Additionally, it can facilitate the connection
between individuals and families with supporting resources such as high-quality, trauma-
informed treatment, which was specifically noted as a need in my research. Although there are
numerous factors that contribute to childhood adversity, it is important to note that ACEs can
occur outside of the home and family unit. This highlights the need for ongoing research and the
implementation of knowledge regarding expanded ACEs, programs that are evidence-based and
trauma-informed, and a multi-system level understanding of ACEs and resilience. Positive social
change can be achieved as a result of the application and success of these types of initiatives,
which can lead to resilience growth at micro, meso, exo, macro, and chronosystem levels.
Delimitations and Limitations
Delimitations and limitations are important aspects of qualitative research that help
define the boundaries and potential weaknesses of a study. Delimitations refer to the boundaries

182
or limits established for a study. These are deliberate decisions made to refine the focus of the
study. Creswell and Poth (2018) indicated that delimitations are essential for establishing the
boundaries of the study, specifying what will be included and what will be excluded. For
instance, one might decide to concentrate on a particular geographic region, historical timeframe,
or demographic group. Delimitations play a crucial role in ensuring that the study remains
manageable and concentrated. Simon and Goes (2013) highlight that delimitations are under the
researcher's influence and are frequently associated with the study's conceptual framework,
research questions, and criteria for participant selection. By clearly stating the delimitations, one
provides context for their findings and helps readers understand the specific conditions under
which the study was conducted.
Limitations represent potential weaknesses in the study that are primarily beyond the
control of the individual conducting the research. These are elements that could influence the
outcomes or the capacity to project the findings. Theofanidis and Fountouki (2018) highlight that
qualitative research frequently encounters limitations concerning validity, reliability, and
generalizability. By recognizing these limitations, scholars exhibit openness and enable readers
to understand the findings within the correct framework. A crucial recognition that although
limitations may influence the study, they do not inherently undermine the validity of the
research. Instead, avenues for further investigation and enhancement in research methods were
identified. Both delimitations and limitations are essential components in qualitative studies, as
they outline the study's boundaries and recognize possible shortcomings.
Delimitations
The delimitations in this study were selected to facilitate data processing and to minimize
outliers in the collected data. I selected the age range for the study to include individuals who are

183
26 years old or older in order to engage a group of participants who have matured beyond
adolescence and have had the opportunity to heal from their trauma. Preliminary unofficial
surveys conducted in preparation for the study indicated that individuals over the age of 26 were
more likely to have healed from their ACEs. The lower limit of the age group was set at 26Oyears
to ensure that participants have had sufficient time to initiate professional engagement regarding
their trauma history, thereby addressing ethical and safety considerations. Furthermore, this
study focused on adults who have encountered childhood trauma and exhibited resilience in their
later years. It excluded individuals who lacked resilience or those who encountered trauma solely
in adulthood. The study focused on individuals who were both willing and capable of sharing
their traumatic experiences and the journey of resilience they experienced. Setting the criteria
may have led to the exclusion of individuals who were hesitant to disclose such personal
information. Participants were chosen according to their self-identified resilience and capacity to
express their experiences, potentially constraining the range of perspectives represented.
Limitations
The small sample size of interviewees restricts the applicability of the findings to the
wider population of trauma survivors. The interviews conducted retrospectively depend on the
memories and perceptions of participants regarding past events, which can be influenced by
recall bias or reinterpretation as time progresses. The investigation did not incorporate
quantitative assessments of resilience or trauma, depending exclusively on qualitative self-
reports from participants. The examination of cultural and demographic factors that could impact
resilience was not conducted systematically among all participants. Participant backgrounds and
potential biases may have influenced the interpretation of the interview data, despite efforts to
maintain objectivity. The study lacked a longitudinal approach with participants, limiting the

184
ability to offer insights into the potential changes in resilience over time or in reaction to new
challenges. When interpreting the data, being aware of delimitations and limitations can be a
form of bracketing for the researcher while considering participant response applicability to
different contexts or populations Creswell and Poth (2018).
Recommendations for Future Research
The targeted population obtained by using snowballOsampling is one of my research's
strengths. Expanding the participant pool would allow for cultural variances as each community
and region across the country have different cultural practices and values. Further study using a
more limited sample population, such as a particular county or community, could offer valuable
insights into the current services offered in the community, uncover areas where services need
more improvement, and assess the effectiveness of efforts to prevent adverse childhood ACE and
enhance resilience within the community. Evaluation of programs in settings such as schools,
mental health centers, children and family services, and faith-based organizations could provide
insight on the systemic barriers identified in my research. Further exploration of the relationship
between specific types of ACEs and resilience development is needed. While this study provided
insights into various traumatic experiences, a more focused examination of how different ACE
categories (e.g., sexual abuse, neglect, household dysfunction) uniquely impact resilience could
yield valuable information for targeted interventions. Longitudinal studies tracking individuals
from childhood through adulthood would provide a more comprehensive understanding of the
resilience development process. Such research could identify critical periods for intervention and
illuminate the long-term effects of various protective factors. Investigation into the role of
cultural and societal factors in resilience development is warranted.

185
Future studies may want to consider how different cultural contexts, social support
systems, and community resources influence an individual's ability to overcome childhood
adversity. More research is needed on the neurobiological aspects of resilience in ACE survivors.
Studies examining brain structure and function in resilient adults with ACE histories could
provide insights into the physiological underpinnings of resilience and potential avenues for
therapeutic interventions. Exploration of the intergenerational transmission of resilience in
families affected by ACEs would be valuable. Understanding how resilient adults who
experienced childhood trauma parent their own children and potentially break cycles of abuse
could inform family-based interventions.
Further investigation into the role of spirituality and faith in resilience development is
recommended. While some participants mentioned the importance of their faith, a more in-depth
study of how spiritual beliefs and practices contribute to resilience could yield important
insights. Research on the effectiveness of various therapeutic approaches in fostering resilience
among ACE survivors is needed. Comparative studies of different treatment modalities could
help identify the most effective interventions for building resilience in this population.
Examination of resilience in diverse populations, including different ethnic, socioeconomic, and
geographic groups, would provide a more comprehensive understanding of resilience across
various contexts and help tailor interventions to specific communities. These recommendations
aim to address gaps in the current research and provide a more nuanced understanding of the
complex relationship between adverse childhood experiences and resilience in adulthood.
Summary
This research explored the lived experiences of individuals in the Pacific Northwest who
demonstrated resilience in adulthood despite having high Adverse Childhood Experiences

186
(ACEs) scores. The primary objective was to gain a deeper understanding of resilience in the
context of ACEs, a crucial area of study given the long-lasting impact of childhood trauma on
adult well-being. By focusing on those who have shown resilience, this study aimed to uncover
the factors that contribute to positive outcomes in the face of significant adversity. Participants in
the study provided valuable insights into the factors that contributed to their resilience. These
personal accounts offered a nuanced perspective on the complex interplay between adverse
experiences and the development of resilience. The qualitative nature of the research allowed for
a rich exploration of individual stories, revealing patterns and themes that might not be captured
in quantitative studies. Phenomenology yielded fresh perspectives that have not been found in
existing literature, contributing to a more comprehensive understanding of resilience in the
context of ACEs. The use of qualitative thematic analysis revealed significant findings regarding
the protective factors that enhanced participant resilience. These factors likely included elements
such as supportive relationships, personal strengths, access to resources, and effective coping
strategies. Understanding these protective factors is crucial for developing interventions and
support systems that can foster resilience in individuals with high ACEs. Additionally, the
research uncovered obstacles that participants encountered in obtaining assistance for addressing
their ACEs. These barriers may have included stigma, lack of awareness, limited access to
services, or systemic challenges in healthcare and social services.
A key implication of this research is the need for trauma-informed services across various
sectors of society. The findings suggest that a comprehensive approach is necessary,
encompassing areas such as education, mental health, religious institutions, justice systems, and
social services. Implementing trauma-informed practices in these sectors can create a more
supportive environment for individuals with high ACEs, potentially mitigating the long-term

187
impacts of childhood adversity and promoting resilience. The findings of this research validate
and extend the conclusions of other studies in the field. They reinforce the importance of timely
interventions to prevent and address ACEs, as well as to foster resilience through protective
factors. This alignment with existing research strengthens the case for implementing evidence-
based practices and policies aimed at supporting individuals with high ACEs. Moreover, the
unique perspectives gained from this study contribute to a more nuanced understanding of
resilience, potentially informing more effective and targeted interventions. This research has
significant implications for policy and practice and underscores the importance of early
identification and intervention for children experiencing adversity. Additionally, the study
highlights the need for ongoing support throughout the lifespan, as resilience is not a fixed trait
but a dynamic process that can be fostered and strengthened over time. The insights gained from
this study can inform the development of more effective prevention programs, intervention
strategies, and support systems for individuals with high ACEs.
In conclusion, this research offers a valuable contribution to the field of ACE and
resilience studies through the exploration through the lived experiences of resilient individuals
with high ACEs. The findings from this study were substantiated by previous studies while also
identifying new insights that can guide future research, policy, and practice. As we continue to
grapple with the long-term impacts of childhood adversity, studies like this play a crucial role in
shaping our understanding and informing our approaches to fostering resilience and well-being.

188
References
AbuHasan, Q., Reddy, V., & Siddiqui, W. (2023). Neuroanatomy, amygdala. InOStatPearls.
StatPearls Publishing.
Arnekrans, A. K., Calmes, S. A., Laux, J. M., Roseman, C. P., Piazza, N. J., Reynolds, J. L.,
Harmening, D., & Scott, H. L. (2018).OCollege students' experiences of childhood
developmental Traumatic stress: Resilience, first-year academic performance, and
substance use.OJournal of College Counseling,O21(1), 2-14.
https://doi.org/10.1002/jocc.12083
Arnsten, A. F. (2009). Stress signalling pathways that impair prefrontal cortex structure and
function.ONature reviews. Neuroscience,O10(6), 410–422. https://doi.org/10.1038/nrn2648
Association, N. a. P. (2013). Diagnostic and Statistical Manual of Mental Disorders.
https://doi.org/10.1176/appi.books.9780890425596
Baglivio, M. T., Wolff, K. T., DeLisi, M., & Jackowski, K. (2020). The role of adverse
childhood experiences (ACEs) and psychopathic features on juvenile offending
Ccriminal careers to age 18.OYouth Violence and Juvenile Justice, 18(4), 337-364.
https://doi.org/10.1177/1541204020927075
Baglivio, M. T., Wolff, K. T., Epps, N., & Nelson, R. (2017). Predicting adverse childhood
experiences: The importance of neighborhood context in youth trauma among
delinquent youth.OCrime & Delinquency, 63(2), 166-188.
https://doi.org/10.1177/0011128715570628
Becker-Blease, K. A., & Freyd, J. J. (2005). Beyond PTSD: An evolving relationship between
trauma theory and family violence research.OJournal of Interpersonal Violence, 20(4),
403–411.Ohttps://doi.org/10.1177/0886260504269485

189
Bellis, M. A., Hughes, K., Ford, K., Hardcastle, K. A., Sharp, C. A., Wood, S., Homolova, L., &
Davies, A. (2018). Adverse childhood experiences and sources of childhood resilience: A
retrospective study of their combined relationships with child health and educational
attendance. BMC Public Health, 18(1), 792.
Bernard, D. L., Calhoun, C. D., Banks, D. E., Halliday, C. A., Hughes-Halbert, C., & Danielson,
C. K. (2020). Making the “C-ACE” for a culturally-informed adverse childhood
experiences framework to understand the pervasive mental health impact of racism on
black youth. Journal of Child & Adolescent Trauma, 14(2), 233–247.
https://doi.org/10.1007/s40653-020-00319-9
Bethell, C. D., Carle, A., Hudziak, J., Gombojav, N., Powers, K., Wade, R., & Braveman, P.
(2017). Methods to assess adverse childhood experiences of children and families:
Toward approaches to promote child well-being in policy and
practice.OAcademic=Pediatrics, 17(7), S51-S69.
https://doi.org/10.1016/j.acap.2017.04.161
Bethell, C. D., Newacheck, P., Hawes, E., & Halfon, N. (2014). Adverse childhood experiences:
Assessing the impact on health and school engagement and the mitigating role of
resilience.OHealth Affairs, 33(12), 2106-2115. https://doi.org/10.1377/hlthaff.2014.0914O
Blodgett, C., & Lanigan, J. D. (2018). The association between adverse childhood experience
(ACE) and school success in elementary school children. School Psychology Quarterly,
33(1), 137–146. https://doi.org/10.1037/spq0000256
Borge, A. I., Motti-Stefanidi, F., & Masten, A. S. (2016). Resilience in developing systems: The
promise of integrated approaches for understanding and promoting positive adaptation.
European Journal of Developmental Psychology, 13(3), 297-312.

190
Borja, S., Nurius, P. S., Song, C., & Lengua, L. J. (2019). Adverse childhood experiences to
adult adversity trends among parents: Socioeconomic, health, and developmental
implications. Children and Youth Services Review, 100, 258-266.
Braveman, P., & Gottlieb, L. (2014). The social determinants of health: It’s time to consider the
causes of the causes. Public Health Reports, 129(1_suppl2), 19–31.
https://doi.org/10.1177/00333549141291s206
Brumley, L. D., Jaffee, S. R., & Brumley, B. P. (2017). Pathways from childhood adversity to
problem behaviors in young adulthood: The mediating role of adolescents' future
expectations.OJournal of youth and adolescence,O46(1), 1–14.
https://doi.org/10.1007/s10964-016-0597-9
Cao, F., Li, J., Xin, W., & Cai, N. (2024). Impact of social support on the resilience of youth:
mediating effects of coping styles. Frontiers in Public Health, 12.
https://doi.org/10.3389/fpubh.2024.1331813
Carr, A. (2022). Trauma. In The handbook of child and adolescent clinical psychology: A
contextual approach. Routledge.
Chen, M., Wang, F., Xie, X., Yang, X., Luo, Y., Zhuang, C., & Xie, B. (2024). Application of
bundled process control in the prevention of pressure injury in patients with head and
neck cancer.OPloS one,O19(6), e0305190. https://doi.org/10.1371/journal.pone.0305190
Collier, L. (2016). Growth after trauma. Monitor on Psychology, 47(10), 48.
Crandall, A., Miller, J. R., Cheung, A., Novilla, L. K., Glade, R., Novilla, M. L. B., Magnusson,
B. M., Leavitt, B. L., Barnes, M. D., & Hanson, C. L. (2019). ACEs and counter-ACEs:
How positive and negative childhood experiences influence adult health. Child Abuse &
Neglect, 96, 104089.

191
Creswell, J., & Poth, C. (2018). Qualitative Inquiry and Research Design: Choosing Among
Five
Approaches. 3rd ed. Los Angeles, CA: Sage.
Cross, D., Fani, N., Powers, A., & Bradley, B. (2017). Neurobiological development in the
context of childhood Trauma.OClinical psychology : a publication of the Division of
Clinical Psychology of the American Psychological Association,O24(2), 111–124.
https://doi.org/10.1111/cpsp.12198
Crouch, E., Probst, J. C., Radcliff, E., Bennett, K. J., & McKinney, S. H. (2019). Prevalence of
adverse childhood experiences (ACEs) among US children. Child Abuse & Neglect, 92,
209–218. https://doi.org/10.1016/j.chiabu.2019.04.010
Daníelsdóttir, S., Sigurðardóttir, S., Þorgeirsdóttir, H., & Hauksdóttir, A. (2022). Adverse
childhood experiences and resilience among adults: A population-based study in Iceland.
Scandinavian Journal of Public Health, 50(1), 74-84.
Dell’Osso, L., Lorenzi, P., Nardi, B., Carmassi, C., & Carpita, B. (2022). Post traumatic growth
(PTG) in the frame of traumatic experiences. PubMed, 19(6), 390–393.
https://doi.org/10.36131/cnfioritieditore20220606
De los Reyes-Aragon, C.OJ., Amar Amar, J., De Castro Correa, A., Lewis Harb, S., Madariaga,
C., & Abello-Llanos, R. (2016). The care and development of children living in
contexts of poverty.OJournal of Child and Family Studies, 25(12), 3637-3643.
https://doi.org/10.1007/s10826-016-0514-6
De Simone, S., Planta, A., & Cicotto, G. (2018). The role of job satisfaction, work engagement,
self-efficacy and agentic capacities on nurses' turnover intention and patient
satisfaction.OApplied Nursing Research, 39, 130-140.

192
https://doi.org/10.1016/j.apnr.2017.11.004
De Souza Morais, R. L., De Castro Magalhães, L., Nobre, J. N. P., Pinto, P. F. A., Da Rocha
Neves, K., & Carvalho, A. M. (2021). Quality of the home, daycare and neighborhood
environment and the cognitive development of economically disadvantaged children in
early childhood: A mediation analysis. Infant Behavior and Development, 64, 101619.
https://doi.org/10.1016/j.infbeh.2021.101619
Doyle, C., & Cicchetti, D. (2017). From the cradle to the grave: The effect of adverse caregiving
environments on attachment and relationships throughout the lifespan. Clinical
Psychology Science and Practice, 24(2), 203–217. https://doi.org/10.1111/cpsp.12192
Dube, B. (2020). Rural online learning in the context of COVID 19 in South Africa: Evoking an
inclusive education approach. Multidisciplinary Journal of Educational Research, 10(2),
135. https://doi.org/10.17583/remie.2020.5607
Felitti, V. J., Anda, R. F., Nordenberg, D., Williamson, D. F., Spitz, A. M., Edwards, V., Koss,
M. P., & Marks, J. S. (1998). Relationship of childhood abuse and household
dysfunction to many of the leading causes of death in adults. American Journal of
Preventive Medicine, 14(4), 245–258. https://doi.org/10.1016/s0749-3797(98)00017-8
Finkelhor, D., Turner, H. A., Shattuck, A., & Hamby, S. L. (2015). Prevalence of childhood
exposure to violence, crime, and abuse: Results from the national survey of children's
exposure to violence.OJAMA pediatrics,O169(8), 746–754.
https://doi.org/10.1001/jamapediatrics.2015.0676
Folkman, S., & Moskowitz, J. T. (2000). Positive affect and the other side of coping.OAmerican
Psychologist, 55(6), 647–654.Ohttps://doi.org/10.1037/0003-066X.55.6.647

193
Friedman, M. J. (2019).OPTSD history and overview. U.S. Department of Veterans Affairs.
Fry, D., Fang, X., Elliott, S., Casey, T., Zheng, X., Li, J., Florian, L., & McCluskey, G. (2018).
The relationships between violence in childhood and educational outcomes: A global
systematic review and meta-analysis. Child Abuse & Neglect, 75, 6-28.
Garmezy, N., & Rutter, M. (1983). Stress, coping, and development in children. McGraw-Hill.
Gray, P., Jump, D., & Smithson, H. (2023b). Adverse childhood experiences. In Policy Press
eBooks (pp. 54–68). https://doi.org/10.1332/policypress/9781529225938.003.0005
Greene, J. D., Sommerville, R. B., Nystrom, L. E., Darley, J. M., & Cohen, J. D. (2014). An
fMRI investigation of emotional engagement in moral judgment. Science, 293(5537),
2105-2108.
Hamby, S., Taylor, E., Mitchell, K., Jones, L., & Newlin, C. (2020). Is it better to seek or to
receive? A dual-factor model of social support.OInternational Journal of Child
and=Adolescent Resilience, 7(1), 5-17. https://doi.org/10.7202/1072584ar
Hardcastle, K., Bellis, M. A., Ford, K., Hughes, K., Garner, J., & Ramos Rodriguez, G. (2018).
Measuring the relationships between adverse childhood experiences and educational and
employment success in England and Wales: Findings from a retrospective study. Public
Health, 165, 106-116.
Harper-Browne, C. (2014). The strengthening families approach and protective factors
framework: Branching out and reaching deeper. Center for the Study of Social Policy.
Harris, M. A. (2018). The relationship between physical inactivity and mental wellbeing:
Findings from a gamification-based community-wide physical activity
intervention.OHealth Psychology Open, 5(1). https://doi.org/10.1177/2055102917753853
Heard-Garris, N. J., Cale, M., Camaj, L., Hamati, M. C., & Dominguez, T. P. (2018).

194
Transmitting trauma: A systematic review of vicarious racism and child health. Social
Science & Medicine, 199, 230-240.
HRSA. (2019). National Survey of Children's Health. Health Resources and Services
Administration, Maternal and Child Health Bureau.
HRSA. (2020). National Survey of Children's Health. Health Resources and Services
Administration, Maternal and Child Health Bureau.
Hughes, K., Bellis, M. A., Hardcastle, K. A., Sethi, D., Butchart, A., Mikton, C., Jones, L., &
Dunne, M. P. (2017). The effect of multiple adverse childhood experiences on health: A
systematic review and meta-analysis. The Lancet Public Health, 2(8), e356-e366.
Hunt, T. K. A., Slack, K. S., & Berger, L. M. (2017). Adverse childhood experiences and
behavioral problems in middle childhood. Child Abuse & Neglect, 67, 391-402.
Ijadi-Maghsoodi, R., Marlotte, L., Garcia, E., Aralis, H., Lester, P., Escudero, P., & Kataoka, S.
(2017). Adapting and implementing a school-based resilience-building curriculum
among low-income racial and ethnic minority students.OContemporary school
psychology,O21(3), 223–239. https://doi.org/10.1007/s40688-017-0134-1
Kelly-Irving, M., & Delpierre, C. (2019). A critique of the adverse childhood experiences
framework in epidemiology and public health: Uses and misuses. Social Policy and
Society, 18(3), 445–456. https://doi.org/10.1017/s1474746419000101
Kolk, B. A., & Bessel, A. (2014). The body keeps the score: Brain, mind, and body in the
healing of trauma. Viking.
Kuffer, M., Pfeffer, K., & Sliuzas, R. (2016). Slums from Space—15 Years of slum mapping
using remote sensing.ORemote Sensing,O8(6), 455. https://doi.org/10.3390/rs8060455
Larkin, H., Felitti, V. J., & Anda, R. F. (2014). Social work and adverse childhood experiences
195
research: Implications for practice and health policy. Social Work in Public Health,
29(1), 1-16.
Larson, S., Chapman, S., Spetz, J., & Brindis, C. D. (2017). Chronic childhood trauma, mental
health, academic achievement, and school-based health center mental health
services.OThe Journal of school health,O87(9), 675–686.
https://doi.org/10.1111/josh.12541
Laverty, S. M. (2003). Hermeneutic phenomenology and phenomenology: A comparison of
historical and methodological considerations. International Journal of Qualitative
Methods, 2(3), 21–35. https://doi.org/10.1177/160940690300200303
Lincoln, Y. S., Guba, E. G., & Pilotta, J. J. (1985). Naturalistic inquiry.OInternational Journal
of=Intercultural Relations, 9(4), 438-439. https://doi.org/10.1016/0147-1767(85)90062-8
Loudermilk, E., Loudermilk, K., Obenauer, J., & Quinn, M. A. (2018). Impact of adverse
childhood experiences (ACEs) on adult alcohol consumption behaviors.OChild abuse &
neglect,O86, 368–374. https://doi.org/10.1016/j.chiabu.2018.08.006
Luthar, S. S., Cicchetti, D., & Becker, B. (2000). The construct of resilience: a critical
evaluation and guidelines for future work. Child Development, 71(3), 543–562.
https://doi.org/10.1111/1467-8624.00164
Martin, L., Oepen, R., Bauer, K., Nottensteiner, A., Mergheim, K., Gruber, H., & Koch, S. C.
(2017). Creative arts interventions for stress management and prevention—a systematic
review. Behavioral Sciences, 8(2), 28.
Masten, A. S. (2001). Ordinary magic: Resilience processes in development.OAmerican
Psychologist, 56(3), 227–238.Ohttps://doi.org/10.1037/0003-066X.56.3.227
Masten, A. S. (2016). Resilience in developing systems: The promise of integrated approaches.

196
European Journal of Developmental Psychology, 13(3), 297-312.
Masten, A. S. (2018). Resilience theory and research on children and families: Past, present, and
promise. Journal of Family Theory & Review, 10(1), 12-31.
Matheson, K., Asokumar, A., & Anisman, H. (2020). Resilience: Safety in the Aftermath of
Traumatic Stressor Experiences. Frontiers in Behavioral Neuroscience, 14.
https://doi.org/10.3389/fnbeh.2020.596919
McInerney, M., & McKlindon, A. (2014). Unlocking the door to learning: Trauma-informed
classrooms & transformational schools. Education Law Center.
McKelvey, K., Baiocchi, M., & Halpern-Felsher, B. (2018). Adolescents’ and young adults’ use
and perceptions of Pod-Based electronic cigarettes. JAMA Network Open, 1(6), e183535.
https://doi.org/10.1001/jamanetworkopen.2018.3535
Merriam, S. B., & Tisdell, E. J. (2016). Qualitative Research: A Guide to Design and
Implementation (4th ed.). San Francisco, CA: Jossey Bass.
Merrick, M. T., Ford, D. C., Ports, K. A., & Guinn, A. S. (2018). Prevalence of adverse
childhood experiences From the 2011-2014 behavioral risk factor surveillance system
in 23 States.OJAMA Pediatrics, 172(11), 1038.
https://doi.org/10.1001/jamapediatrics.2018.2537
Merrick, M. T., Ford, D. C., Ports, K. A., Guinn, A. S., Chen, J., Klevens, J., Metzler, M., Jones,
C. M., Simon, T. R., Daniel, V. M., Ottley, P., & Mercy, J. A. (2019). Vital signs:
Estimated proportion of adult health problems attributable to adverse childhood
experiences and implications for preventionO— 25 States, 2015-2017.OMMWR. Morbidity
and Mortality Weekly Report, 68(44), 999-1005.
https://doi.org/10.15585/mmwr.mm6844e1
197
Merrick, M. T., Ports, K. A., Ford, D. C., Afifi, T. O., Gershoff, E. T., & Grogan-Kaylor, A.
(2017). Unpacking the impact of adverse childhood experiences on adult mental
health.OChild Abuse & Neglect, 69, 10-19. https://doi.org/10.1016/j.chiabu.2017.03.016
Metzler, M., Merrick, M. T., Klevens, J., Ports, K. A., & Ford, D. C. (2016). Adverse childhood
experiences and life opportunities: Shifting the narrative. Children and Youth Services
Review, 72, 141–149. https://doi.org/10.1016/j.childyouth.2016.10.021
Miles, M. B., Huberman, M. A., & Saldaña, J. (2020).OQualitative data analysis: A methods
sourcebook. Sage Publications.
Moeller-Saxone, K., Davis, E., Stewart, D. E., Diaz-Granados, N., & Herrman, H. (2014).
Promoting resilience in adults with experience of intimate partner violence or child
maltreatment: a narrative synthesis of evidence across settings. Journal of Public Health,
37(1), 125–137. https://doi.org/10.1093/pubmed/fdu030
Moisoglou, I., Katsiroumpa, A., Prasini, I., Gallos, P., Kalogeropoulou, M., & Galanis, P.
(2024). Innovation support reduces quiet quitting and improves innovative behavior
and innovation outputs among nurses in Greece. Nursing Reports, 14(4), 2618–2628.
https://doi.org/10.3390/nursrep14040193
Moses, J. O., & Villodas, M. T. (2017). The potential protective role of peer relationships on
school engagement in at-risk adolescents. Journal of Youth and Adolescence, 46(11),
2255-2272.
Moss, E. L., Maghini, D. G., & Bhatt, A. S. (2020). Complete, closed bacterial genomes from
microbiomes using nanopore sequencing. Nature Biotechnology, 38(6), 701–707.
https://doi.org/10.1038/s41587-020-0422-6
Moustakas, C. (1994). Phenomenological research methods. SAGE Publications.

198
Naeem, K., Asghar, S., Griffiths, M. D., & Asad, N. (2023). Adverse childhood experiences and
resilience: A systematic review. Trauma, Violence, & Abuse, 24(2), 477-492.
Newsom, K., & Myers-Bowman, K. (2017). "I am not a victim. I am a survivor": Resilience as a
journey for female survivors of child sexual abuse. Journal of Child Sexual Abuse, 26(8),
927-947.
Nishimi, K., Choi, K. W., Cerutti, J., Powers, A., Bradley, B., & Dunn, E. C. (2020). Measures
of adult psychological resilience following early-life adversity: How congruent are
different measures? Psychological Medicine, 1-10.
Nishimi, K., Choi, K. W., Davis, K. A., Powers, A., Bradley, B., & Dunn, E. C. (2021). Features
of childhood maltreatment and resilient capacity in adulthood: Results from a large
community-based sample. Journal of Psychiatric Research, 134, 1-9.
Oh, D. L., Jerman, P., Silvério Marques, S., Koita, K., Purewal Boparai, S. K., Burke Harris, N.,
& Bucci, M. (2018). Systematic review of pediatric health outcomes associated with
childhood adversity. BMC Pediatrics, 18(1), 83.
Oshri, A., Gray, J. C., Owens, M. M., Liu, S., Duprey, E. B., Sweet, L. H., & MacKillop, J.
(2019). Adverse childhood experiences and amygdalar reduction: High-Resolution
segmentation reveals associations with subnuclei and psychiatric outcomes. Child
Maltreatment, 24(4), 400–410. https://doi.org/10.1177/1077559519839491
Pargament, K. I., & Cummings, J. (2010). Anchored by faith: Religion as a resilience factor. In J.
W. Reich, A. J. Zautra, & J. S. Hall (Eds.),OHandbook of adult resilienceO(pp. 193–210).
The Guilford Press.
Patton, M. Q. (2015).OQualitative research & evaluation methods: Integrating theory and
practiceO(4th ed.). SAGE Publications.

199
Pollak, S. D., & Wolfe, B. L. (2020). How developmental neuroscience can help address the
problem of child poverty.ODevelopment and psychopathology,O32(5), 1640–1656.
https://doi.org/10.1017/S0954579420001145
Poole, J. C., Dobson, K. S., & Pusch, D. (2018). Do adverse childhood experiences predict adult
interpersonal difficulties? The role of emotion dysregulation.OChild abuse & neglect,O80,
123–133. https://doi.org/10.1016/j.chiabu.2018.03.006
Ports, K. A., Ford, D. C., Merrick, M. T., & Guinn, A. S. (2020). ACEs: Definitions,
measurement, and prevalence. In G. J. G. Asmundson & T. O. Afifi (Eds.),OAdverse
childhood experiences: Using evidence to advance research, practice, policy, and
preventionO(pp. 17-34). Elsevier.Ohttps://doi.org/10.1016/b978-0-12-816065-7.00002-1
Radcliff, E., Crouch, E., Strompolis, M., & Srivastav, A. (2019). Homelessness in childhood and
Adverse Childhood Experiences (ACEs). Maternal and Child Health Journal, 23(6),
811–820. https://doi.org/10.1007/s10995-018-02698-w
Ravitch, S., & Carl, N. M. (2016). Qualitative Research: Bridging the Conceptual, Theoretical,
and Methodological. Sage Publications.
Rosenthal, N., Cao, Z., Gundrum, J., Sianis, J., & Safo, S. (2020). Risk factors associated with
In-Hospital mortality in a US national sample of patients with COVID-19. JAMA
Network Open, 3(12), e2029058. https://doi.org/10.1001/jamanetworkopen.2020.29058
Rousseau, D. (2023). Adverse childhood experiences and sources of childhood resilience: A
study of their combined relationships with child health and educational attendance. BMC
Public Health, 18(1), 792.
Ryan, K., Lane, S. J., & Powers, D. (2018). A multidisciplinary model for treating complex

200
trauma in early childhood. International Journal of Play Therapy, 26 (2), 111-123.
Sacks, V., Murphey, D., & Moore, K. (2014). Adverse childhood experiences: National and
state-level prevalence. Child Trends, 28, 1-11.
Salinas-Miranda, A. A., Salemi, J. L., King, L. M., Baldwin, J. A., Berry, E.OL., Austin, D. A.,
Scarborough, K., Spooner, K. K., Zoorob, R. J., & Salihu, H. M. (2015). Adverse
childhood experiences and health-related quality of life in adulthood: revelations from a
community needs assessment.OHealth and Quality of Life Outcomes, 13(1).
https://doi.org/10.1186/s12955-015-0323-4
Schlumpf, Y. R., Nijenhuis, E. R. S., Klein, C., Jäncke, L., & Bachmann, S. (2021). Resting-state
functional connectivity in patients with a complex PTSD or complex dissociative
disorder before and after inpatient trauma treatment.OBrain and Behavior, 11(7).
Sciaraffa, M. A., Zeanah, P. D., & Zeanah, C. H. (2018). Understanding and promoting
resilience in the context of adverse childhood experiences. Early Childhood Education
Journal, 46(3), 343-353.
Shaffer, T.O(2024). Childhood adversity andOlow resilience mayOincrease oddsOof
depression,Oanxiety in pregnancy.OTPMG Excellence.
Sheffler, J. L., Stanley, I., & Sachs-Ericsson, N. (2020). ACEs and mental health outcomes. In G.
J. G. Asmundson & T. O. Afifi (Eds.),OAdverse childhood experiences: Using evidence to
advance research, practice, policy, and preventionO(pp. 47-69).
Elsevier.Ohttps://doi.org/10.1016/b978-0-12-816065-7.00004-5
Simon, M. K., & Goes, J. (2013). Scope, limitations, and delimitations. Dissertation and
scholarly research: Recipes for success.

201
Sloan, A., & Bowe, B. (2014). Phenomenology and hermeneutic phenomenology: the
philosophy, the methodologies, and using hermeneutic phenomenology to investigate
lecturers' experiences of curriculum design.OQuality & Quantity, 48(3), 1291-1303.
https://doi.org/10.1007/s11135-013-9835-3
Souers, K., & Hall, P. (2016). Fostering resilient learners: Strategies for creating a trauma-
sensitive classroom. ASCD.
Southwick, S. M., Bonanno, G. A., Masten, A. S., Panter-Brick, C., & Yehuda, R. (2014).
Resilience definitions, theory, and challenges: Interdisciplinary perspectives. European
Journal of Psychotraumatology, 5(1), 25338.
Statman-Weil, K. (2016).OCreating trauma sensitive classrooms. Academia.edu.
Steele, H., Bate, J., Steele, M., Dube, S. R., Danskin, K., Knafo, H., Nikitiades, A., Bonuck, K.,
Meissner, P., & Murphy, A. (2016). Adverse childhood experiences, poverty, and
parenting stress.OCanadian Journal of Behavioural Science / Revue canadienne
des=sciences du comportement, 48(1), 32-38. https://doi.org/10.1037/cbs0000034O
Stinson, J. D., Quinn, M. A., & Levenson, J. S. (2016). The impact of trauma on the onset of
mental health symptoms, aggression, and criminal behavior in an inpatient psychiatric
sample.OChild Abuse & Neglect, 61, 13-22. https://doi.org/10.1016/j.chiabu.2016.09.005
Struck, S., Stewart-Tufescu, A., Asmundson, A. J.ON., Asmundson, G. G. J., & Afifi, T. O.
(2021). Adverse childhood experiences (ACEs) research: A bibliometric analysis of
publication trends over the first 20 years.OChild Abuse & Neglect, 112, 104895.
https://doi.org/10.1016/j.chiabu.2020.104895
Substance Abuse and Mental Health Services Administration-Health Resources and Services
Administration. (2019). Trauma-informed care in behavioral health services. Treatment

202
Improvement Protocol (TIP) Series 57. HHS Publication No. (SMA) 13-4801.
Theofanidis, D., & Fountouki, A. (2018). Limitations and delimitations in the research
process.OPerioperative Nursing, 7(3), 155-163.
van Breda, A. D. (2018). A critical review of resilience theory and its relevance for social work.
Social Work, 54(1), 1-18
van der Kolk, B. A. (2014). The body keeps the score: Brain, mind, and body in the healing of
trauma. Penguin Books.
Vig, J., Gehrmann, S., Belinkov, Y., Qian, S., Nevo, D., Singer, Y., & Shieber, S.
(2020).OCausal
mediation analysis for interpreting neural NLP: The case of gender bias.
arXiv.Ohttps://arxiv.org/abs/2004.12265
Wade, R., Jr., Shea, J. A., Rubin, D., & Wood, J. (2014). Adverse Childhood Experiences of
Low-Income Urban Youth.OPediatrics, 134(1), e13-e20.
https://doi.org/10.1542/peds.2013-2475
Waite, R., & Ryan, R. A. (2019).OAdverse childhood experiences: What students and health
professionals need to know. Routledge.Ohttps://doi.org/10.4324/9780429261206
Walsh, D., McCartney, G., Smith, M., & Armour, G. (2019). Relationship between childhood
socioeconomic position and adverse childhood experiences (ACEs): a systematic review.
Journal of Epidemiology & Community Health, 73(12), 1087–1093.
https://doi.org/10.1136/jech-2019-212738
Wekerle, C., Hattermann, T., Wang, Q., Crews, L., Von Appen, W., & Danilov, S. (2020).
Properties and dynamics of mesoscale eddies in Fram Strait from a comparison between
two high-resolution ocean–sea ice models. Ocean Science, 16(5), 1225–1246.

203
https://doi.org/10.5194/os-16-1225-2020
Werner, E. E. (1989). High-risk children in young adulthood: a longitudinal study from birth to
32 years.OThe American journal of orthopsychiatry,O59(1), 72–81.
Werner, E. E., & Smith, R. S. (1992).OOvercoming the odds: High risk children from birth to
adulthood.=Cornell University Press.
WestEd. (2004). Resilience: A Universal Capacity. https://www2.wested.org/www-
static/online_pubs/resiliency/resiliency.chap1.pdf
Woods-Jaeger, B. A., Cho, B., Sexton, C. C., Slagel, L., & Goggin, K. (2018). Promoting
resilience: Breaking the intergenerational cycle of adverse childhood experiences. Health
Education & Behavior, 45(5), 772-780.
Zandi, H., Amirinejhad, A., Azizifar, A., Aibod, S., Veisani, Y., & Mohamadian, F. (2021). The
effectiveness of mindfulness training on coping with stress, exam anxiety, and happiness
to promote health.OJournal of education and health promotion,O10(1), 177.
https://doi.org/10.4103/jehp.jehp_616_20
Zhen-Duan, J., Jacquez, F., & Vaughn, L. (2023). Adverse childhood experiences and resilience:
A qualitative exploration of Hispanic emerging adults' experiences. Emerging Adulthood,
11(1), 194-208.

LIBERTY
UNIVERSITY.
INSTITUTIONAL
REVIEW
BOARD
October
30,
2024
Rebecca
Anderson
Jason
Ward
Re:
IRB
Exemption
-
IRB-FY24-25-417
A
qualitative
Study
Exploring
the
Effects of
Adverse
Childhood
Experiences
‘on
Development
and
the
Role
of
Resilience
in
Shaping
Adult
Life.
Dear
Rebecca
Anderson,
Jason
Ward,
‘The
Liberty
University
Institutional
Review
Board
(IRB)
has
reviewed
your
application
per
the
Office
for
Human
Research
Protections
(OHRP)
and
Food
and
Drug
Administration
(FDA)
regulations
and
finds
your
study
to
be
‘exempt
from
further
IRB
review.
This
means
you
may
begin
your
research
with
the
data-safeguarding
methods
described
in
your
IRB
application,
and
no
further
IRB
oversight
is
required.
Your
study
falls
under
the
folowing
exemption
category,
which
identifies
specific
situations
in
which
human
participants
research
is
exempt
from
the
policy
set
forth
in
45
CFR
46:104(4):
Category
2.(ii).
Research
that
only
includes
interactions
involving
educational
tests
(cognitive,
diagnostic,
aptitude,
achievement),
survey
procedures,
interview
procedures,
or
observation
of public behavior
(including
visual
or
‘auditory
recording)
if
at
least
one
of
the
following
criteria
is
met:
‘The
information
obtained
is
recorded
by
the
investigator
in
such a
manner
that
the
identity
of
the
human
subjects
can
readily
be
ascertained,
directly
or
through
identifiers
linked
to
the
subjects,
and
an IRB
conducts
a
limited
IRB
review
to
make
the
determination
required
by
§46.111(a)(7).
For a
PDF
of
your
exemption
letter,
click
on
your
study
number
in
the
My
Studies
card
on
your
Cayuse
dashboard
Next,
cick
the
Submissions
bar
beside
the
Study
Details
bar
on
the
Study
Details page.
Finally,
click
Initial
under
Submission
Type
and
choose
the
Letters
tab
toward
the bottom
of
the
Submission
Details
page.
Your
information
sheet
and
final
versions
of
your
study
documents,
which
you
must
use
to
conduct your
study,
can
also
be
found
on
the
same
page
under
the
Attachments
tab.
‘This
exemption
only
applies
to
your
current
research
application,
and
any
modifications
to
your
protocol
must
be
reported
to
the
Liberty
University
IRB
for
verification
of
continued
exemption
status.
You
may
report
these
changes
by completing
modification
submission
through
your
Cayuse
IRB
account.
If
you
have
any
qusstions
about
this exemption
or
need
assistance
in
determining
whether
possible
modifications
to
‘your
protocol
would
change
your
exemption
status,
please
email
us
at irb@liberty
edu
Sincerely,
G.
Michele
Baker,
PhD,
CIP
Administrative
Chair
Reooarch
Ethics
Offioo
204
Appendix A: IRB Approval

205
Appendix B: Social Media Recruitment
Social Media Recruit Post
ATTENTION: I am conducting research as part of the requirements for a Doctor of Education
degree at Liberty University. The purpose of my research is to investigate the lived experiences
of adults who have overcome childhood trauma and have demonstrated resilience in adulthood.
Additionally, I am writing to invite eligible participants to join my study. Eligible participants
must meet the following criteria:
Participants must be 26 years of age or older and have suffered chronic childhood trauma
(ongoing trauma or more than four traumatic events in childhood).
Participants must have moved beyond the trauma and have attained resiliency in
adulthood.
Eligible participants will be asked to participate in a video-recorded Zoom interview (60
minutes) and review their interview transcripts for accuracy (30 minutes). Names and other
identifying information will be requested as part of this study, but the information will remain
confidential.
To participate, please contact Rebecca Anderson via phone on 360-910-0126. You will be
emailed a link to a screening survey. A consent document will be emailed to you if you meet the
study criteria. The consent document contains additional information about my research. If you
choose to participate, you will be asked to provide an electronic signature. Once you’ve applied
your signature, the document will be automatically returned to the researcher.

Title
of
the
Project:
A
Qualitative
Study
Exploring
the
Effects
of Adverse
Childhood
Experiences
on
Development
and
the
Role
of
Resilience
in
Shaping
Adult
Life
Principal
Investigator:
Rebecca
Anderson,
Doctoral
Candidate,
Community
Care and
Consent
‘Counseling
Department,
Liberty
University
‘Key
Information
about
the
Research
Study
‘You
are
invited
to
participate
in
a
research
study.
Eligible
participants
must
meet
the
following
‘Things
Participants
must
be
26
years
of
age
or
older
and
have
suffered
chronic
childhood
trauma
(ongoing
trauma
or
more
than
four
traumatic
events
in
childhood).
Participants
must
have
moved
beyond
the
trauma
and
have
attained
resiliency
in
‘adulthood,
you
should
know:
‘The
purpose
of
my
research
isto
investigate
the
lived
experiences
of
adults
who
have
‘overcome
childhood
trauma
and
have
demonstrated
resilience
in
adulthood. If
you
choose
to
participate,
you
will
be
asked
to
an
online
zoom
interview
will
take
approximately
60
minutes,
‘Taking
part
in
this
research
project
is
voluntary.
You
do
not
have
to
participate,
and
you
‘can
stop
at
any
time.
Please
read
this
entire
form and
ask
questions
before
deciding
whether
to
participate
in
this,
research.
‘What
is
the
study
about
and
why
is
it
being
done?
‘The
purpose
of
the
study
is
to
investigate
the
lived
experiences
of
adults
who
have
overcome
childhood
trauma
and
have
demonstrated
resilience
in
adulthood,
‘What
will
happen
if
you
take
part
in
this
study?
If
you
agree
to
be
in this
study,
I
will
ask
you
to
do
the
following:
1
Ifyou
agree
to
participate
in
the study,
you
will
be
asked
to
join
a
one-on-one
interview
‘via
Zoom
for
45-60
minutes.
After
the
interview,
you
will
be
asked
to
confirm
the
accuracy
of
interview
transcripts
via
email
Liberty
University
IRB-FY24-25-417
[Approved
on
10-30-2024
206
Appendix C: Consent

‘How
could
you
or
others
benefit
from
this
study?
Participants
should
not
expect
a
direct
benefit
from
participating
in
this
study.
Benefits
to
society
include
the
opportunity
to
facilitate
the
development
ofprograms
for
children
‘and
adults
who
have
endured
childhood
trauma
and
adversity
(ae
eee
a]
|
‘The
expected
risks
from
participating
in
this
study
are
minimal,
which
means
they
are
equal
to
the
risks
you
would
encounter
in
everyday
life.
The
risks
involved
in this
study
include
the
possibility
of
psychological
stress
from
being asked
to
recall
and
discuss
prior
trauma.
To
reduce
tisk,
will
deseribe
the steps
I
wll
take
to
mitigate
the
risks,
which
would
include
monitoring
participants,
discontinue
the interview
if
need,
and
provide
referral
information
for
counseling
ee
pS
TETT
|
‘The
records
of
this
study
will
be
kept
private.
Published
reports will not
include
any
information
that
will
make
it
possible
to
identify
a
subject.
Research
records
will
be
stored
securely,
and
only
the
researcher
will
have
access
to
the
records.
‘*
Participant
responses
will
be
kept
confidential
by
replacing
names
with
pseudonyms.
‘©
Interviews
will
be
conducted
in
a
location
where
others
will
not
easily
overhear
the
conversation.
‘*
Data
will
be
stored
on
a
password-locked
computer.
The
researcher
will
have
access
to
the
data,
Affer
three
years,
all
electronic
records
will
be
deleted.
‘*
Recordings
will
be
stored
on
a password
locked
computer.
The
researcher
will
have
‘access
to
the
recordings.
After
one
year, the
recordings
will
be
deleted.
Ts
study
participation
voluntary?
Participation in
this
study
is
voluntary.
Your
decision
whether
to
participate
will not
affect
your
‘current
or
future
relations
with
Liberty
University.
If
you
decide
to
participate,
you
are
free
not
to
answer any
question
or
withdraw
at
any
time
without
affecting
those
relationships.
‘What
should
you
do
if
you
decide
to
withdraw
from
the
study?
Ifyou
choose
to
withdraw from
the
study,
please
contact
the
researcher
at
the
email
address
included
in the
next
paragraph.
Should
you
choose
to
withdraw,
data
collected
from
you
will
be
destroyed
immediately
and
will
not
be
included
in
this
study.
‘Whom
do
you
contact
if
you
have
questions
or
concerns
about
the
study?
Liberty
University
IRB-FY24-25.417
[Approved
on
10-30-2024
207

‘The
researcher
conducting
this
study
is
Rebecca
Anderson.
You may
ask
any
questions
you
have
now.
If
you have
questions
later,
you
are
encouraged
to
contact
her
at
rhooper
@liberty.edu
‘You
may
also
contact
the
researcher's
faculty
sponsor,
Dr.
Ward,
at
‘Whom
do
you
contact
if
you
have
questions
about
your
rights
axa
research
pariipant?
|
Ifyou
have
any
questions
or
concerns
regarding
this
study
and
want
to
talk
to
someone
other
than
the
researcher,
you
are
encouraged
to
contact
the IRB.
Our
physical
address
is
Institutional
Review
Board, 1971
University
Blvd.,
Green
Hall
Ste.
2845,
Lynchburg,
VA,
24515;
our
phone
‘number
is
434-592-5530,
and
our
email
address
is
Disclaimer:
The
Instiwional
Review
Board
(IRB)
ensures
that
human
subjects
research
will
be
‘conducted
ethically
as
defined
and
required by
federal
regulations.
The
topics
covered
and
viewpoints
expressed
or
alluded
to
by
student
and
faculty
researchers are those
ofthe
researchers
and do
not
necessarily
reflect
theofficial
policies
or
postions
of
Liberty
University.
‘Your
Consent
‘By
signing
this
document,
you
are
agreeing
to
be
in
this
study.
Make
sure
you
understand
what
the
study
is
about
before
you
sign.
You
will
be
given
a copy
of
this
document
for
your
records.
‘The
researcher
will
keep
a
copy
of
the
study
records.
If
you
have
any
questions
about
the
study
affer
you
sign
this
document,
you
can
contact
the
study
team
using
the
information
provided
above.
Thave
read
and
understood
the
above
information.
I
have asked
questions
and
have
received
‘answers.
I
consent
to
participate
in
the
study.
The
researcher
has
my
permission
to
video-record
me
as
part
of
my
participation
inthis
study.
Printed
Subject
Name
Signature
&
Date
Liberty
University
IRB-FY24-25-417
[Approved
on
10-30-2024
208

209
Appendix D: Interview Questions
1. What does resilience mean to you?
2. In your experience of resilience, what parts of your personality or sense of self have been
most important?
3. What external factors have had the most significant impact on your resilience?
4. How do you cope with stress?
5. Why did you persevere in the face of hardship when you had every reason to give up?
6. What goals did you have that enabled you to endure hardship?
7. When did you make the decision to shift your focus and refuse to live as a victim?O
8. What resources did you use as a child to deal with or overcome the challenges you faced?
What factors contributed to the availability and accessibility of these resources?
9. What resources have you utilized as an adult to manage or overcome the challenges you
faced? What factors contributed to the availability and accessibility of these resources?
10. What resources do you wish you had available to help you?
11. Can you explain the psychology and emotional impact of your adverse childhood
experiences?
12. In what ways might the ACEs you went through still affect you? in your relationships,
emotionally, mentally, physically, sexually, etc.
13. What enabled you to overcome those challenges?
14. How did your relationship with Christ play a role in your transformation?
15. How did you manage to overcome these challenges?
16. Do you have any further information you would like to include?
17. Can I contact you if I have any more questions or need clarification?

4.
Did
you
feel
that
you
didn’t
have
enough
to
eat,
had
to
wear
dirty
clothes,
or
had
no
one
to
protect
or
take
care
of
you?
2.
Did
you
lose
a parent
through
divorce,
abandonment,
death,
or
other
reason?
3.
Did
you
live
with
anyone
who
was
depressed,
mentally
ill,
or
attempted
suicide?
4,
Did
you
live
with
anyone
who
had
a
problem
with
drinking
or
using
drugs,
including
prescription
drugs?
5.
Did
your
parents
or
adultsin
your
home
ever
hit,
punch,
beat,
or
threaten
to
harm
each
other?
6.
Did
you
live
with
anyone
who
went
to
jail
or
prison?
7.
Did
a
parent
or
adult
in
your
home
ever
swear
at
you,
insult
you,
or
put
you
down?
8.
Did
a
parent
or
adult
in
your
home
ever
hit,
beat,
kick,
or
physically
hurt
you
in
any
way?
9.
Did
you
feel
that
no
one
in
your
family
loved
you
or
thought
you
were
special?
10.
Did
you
experience
unwanted
sexual
contact
(such
as
fondling
or
oral/anal/vaginal
intercourse/penetration)?
DOJO
OOO]
JOO
Your
ACE
score
is
the
total
number
of
checked
responses
Do
you
believe
that
these experiences
have
affected
your
health?
Qyeot
‘Much,
COsome
Or
Lot
210
Appendix E: Survey Questions (ACEs and Resilience)

Item
no.
Oo
AIN
OD
a
fi
WIND
=/]/a]/a
N}>]o
Description
Able
to
adapt
to
change
Close
and
secure
relationships
Sometimes
fate
or
God
can
help
Can
deal
with
whatever
comes
Past
success
gives
confidence
for
new
challenge
See
the
humorous
side
of
things
Coping
with stress
strengthens
Tend
to
bounce
back
after
illness
or
hardship
Things
happen
for
a
reason
Best
effort
no
matter
what
You
can
achieve
your
goals
When
things
look
hopeless,
|
don't
give
up
211

13
14
15
16
17
18
19
20
21
22
23
24
25
Know
where
to
turn
to
for
help
Under
pressure,
focus
and
think
clearly
Prefer
to
take
the
lead
in
problem
solving
Not
easily
discouraged
by
failure
Think
of
self
as
strong
person
Make
unpopular
or
difficult
decisions
Can
handle
unpleasant
feelings
Have
to
act
on a
hunch
Strong
sense
of
purpose
In
control
of
your
life
|
like
challenges
You
work
to
attain
your
goals
Pride
in
your
achievements
212
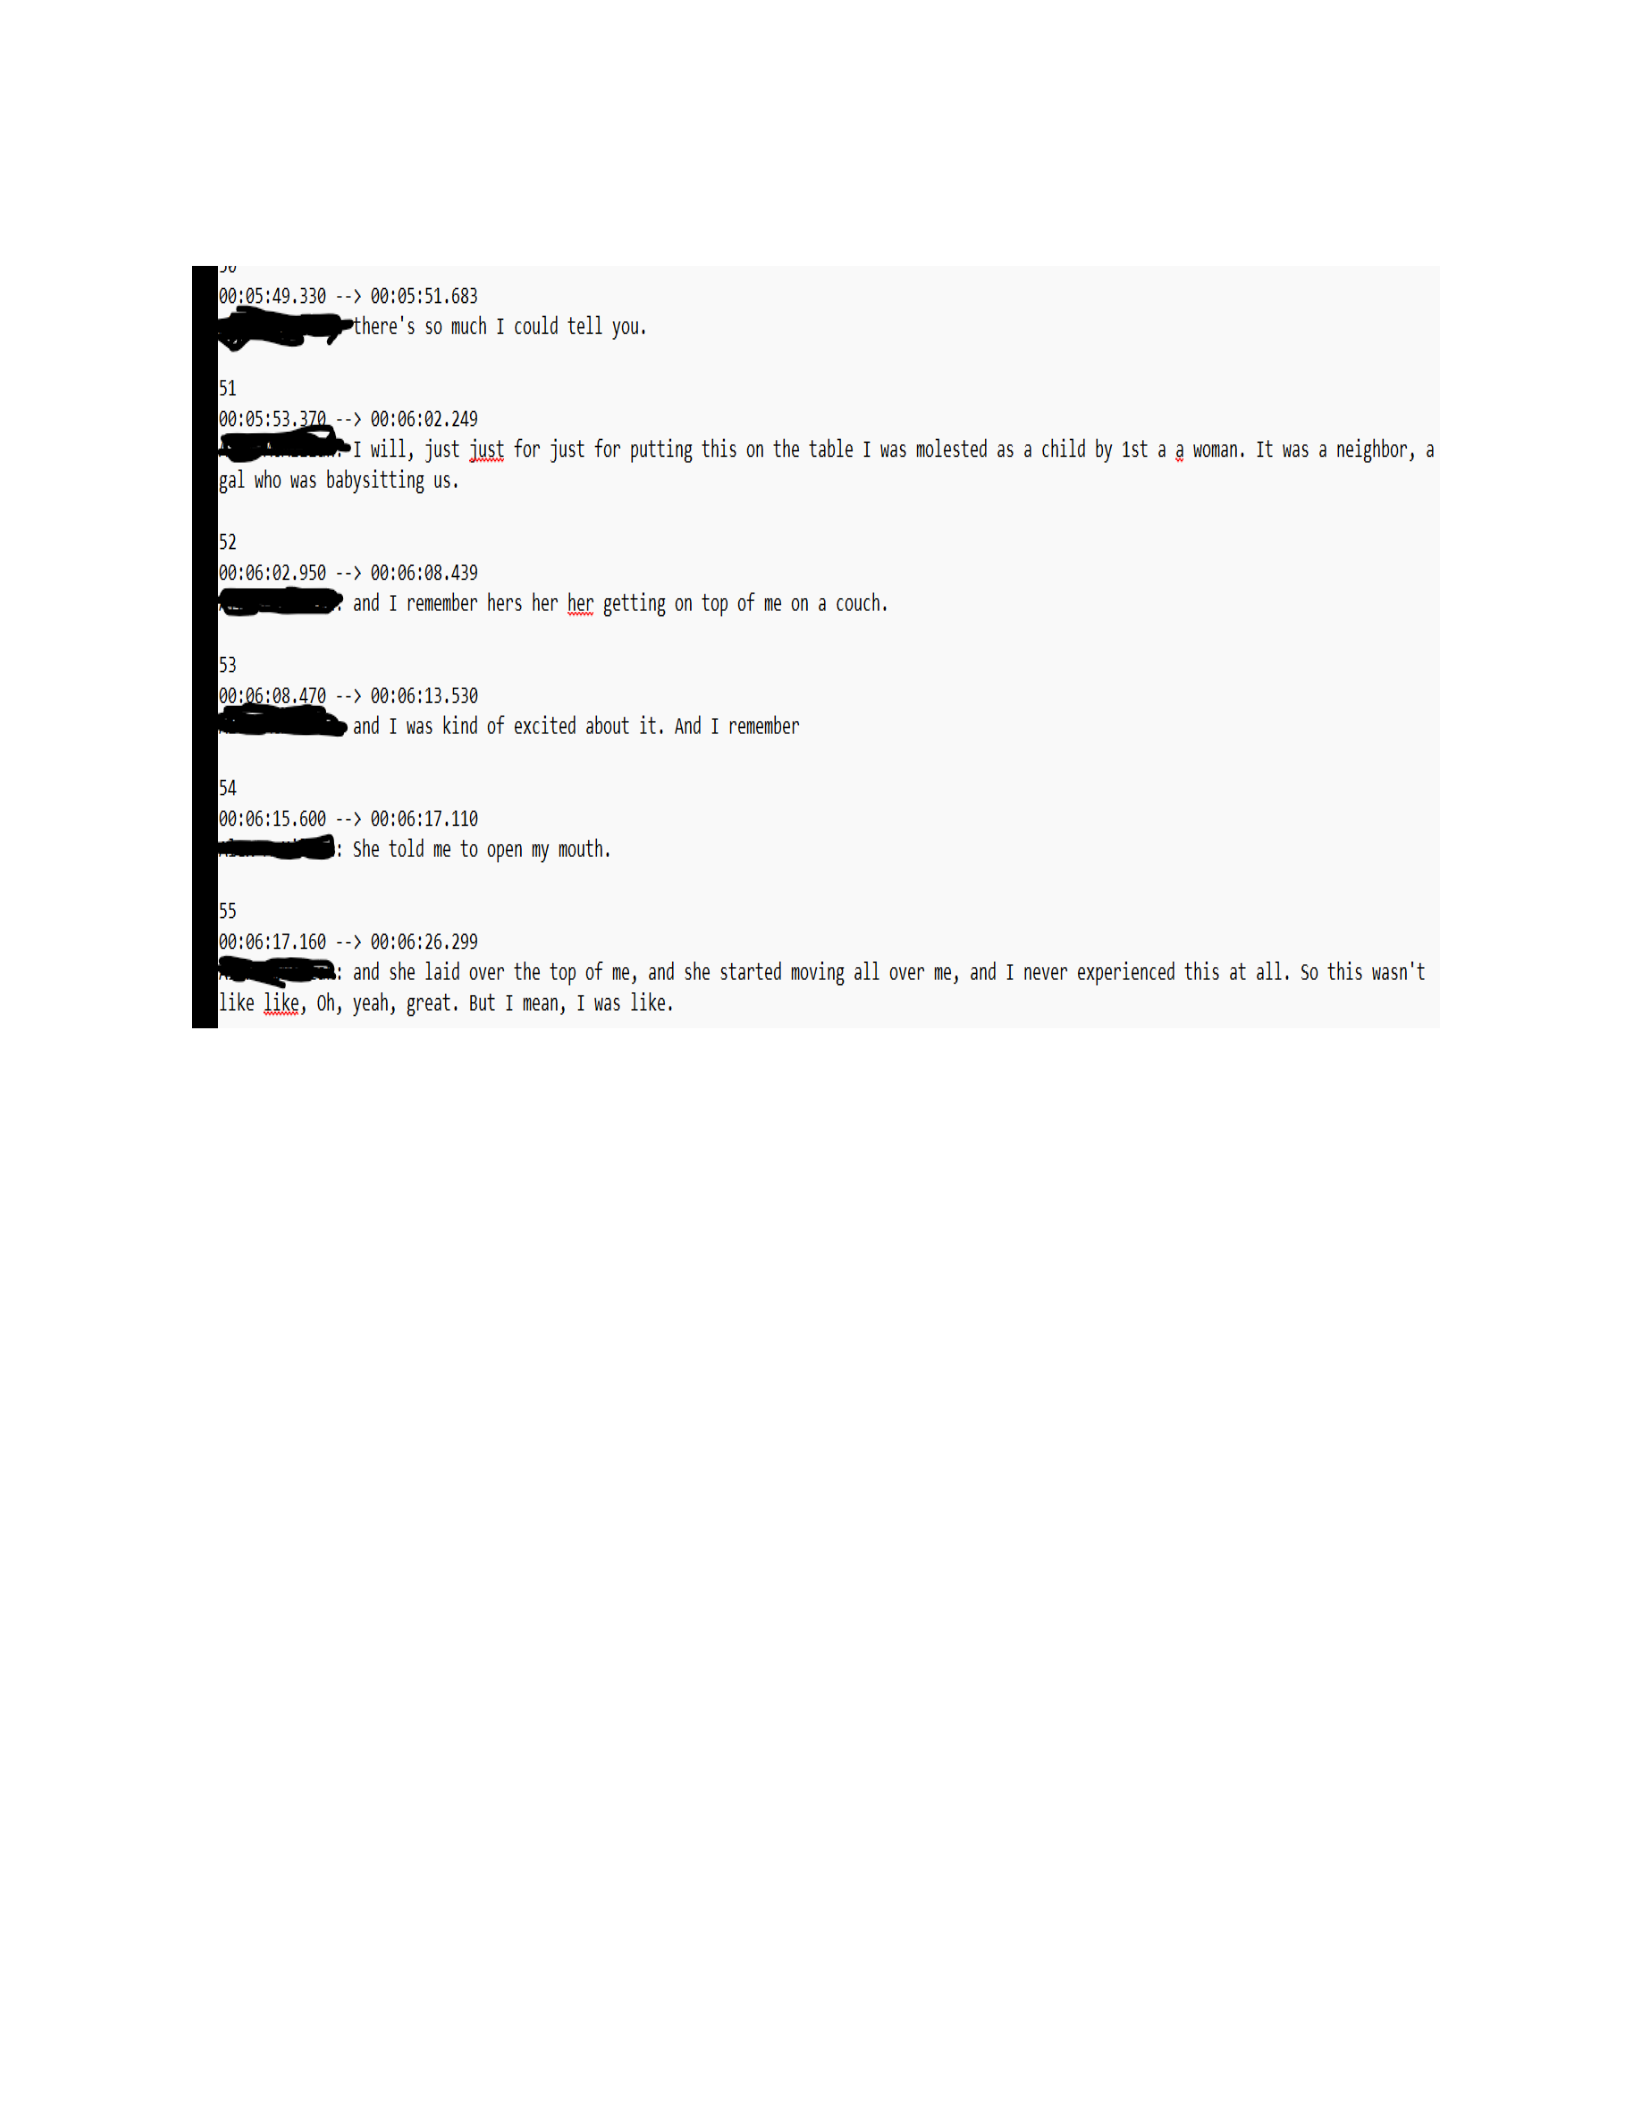
we
nnnnp--
------
ee
He
e-
---p
-
au
00:05:49,330
-->
00:05:51,683
here's
so
much
I
could
tell
you.
51
00:05:53.
-->
00:06:02.249
ute.
will,
just
just
for
just
for
putting
this
on
the
table
I
was
molested
as
a
child
by
1st
a
a
woman,
It
was
a
neighbor,
a
gal
who was
babysitting
us.
52
00:06:02,950
-->
00:06:08.439
GE
anc
1
venenber hers
her
her
getting
on
top
of
me on
a
couch,
53
00:06:08,470
-->
00:05:13,530
aa,
.:
I
was
kind of
excited
about
it.
And
I
remember
54
Q0:@6:15.60@
-->
00:05:17,110
Samm:
she
told
me
to open
my
mouth.
55
00:06:17,160
-->
00:06:26,299
;
and
she
laid over
the top
of
me,
and she
started
moving
all
over
me,
and
I
never
experienced
this
at all. So
this
wasn't
like
like,
Oh,
yeah,
great.
But
I
mean,
I
was
like.
213
Appendix F: Sample Interview Transcript
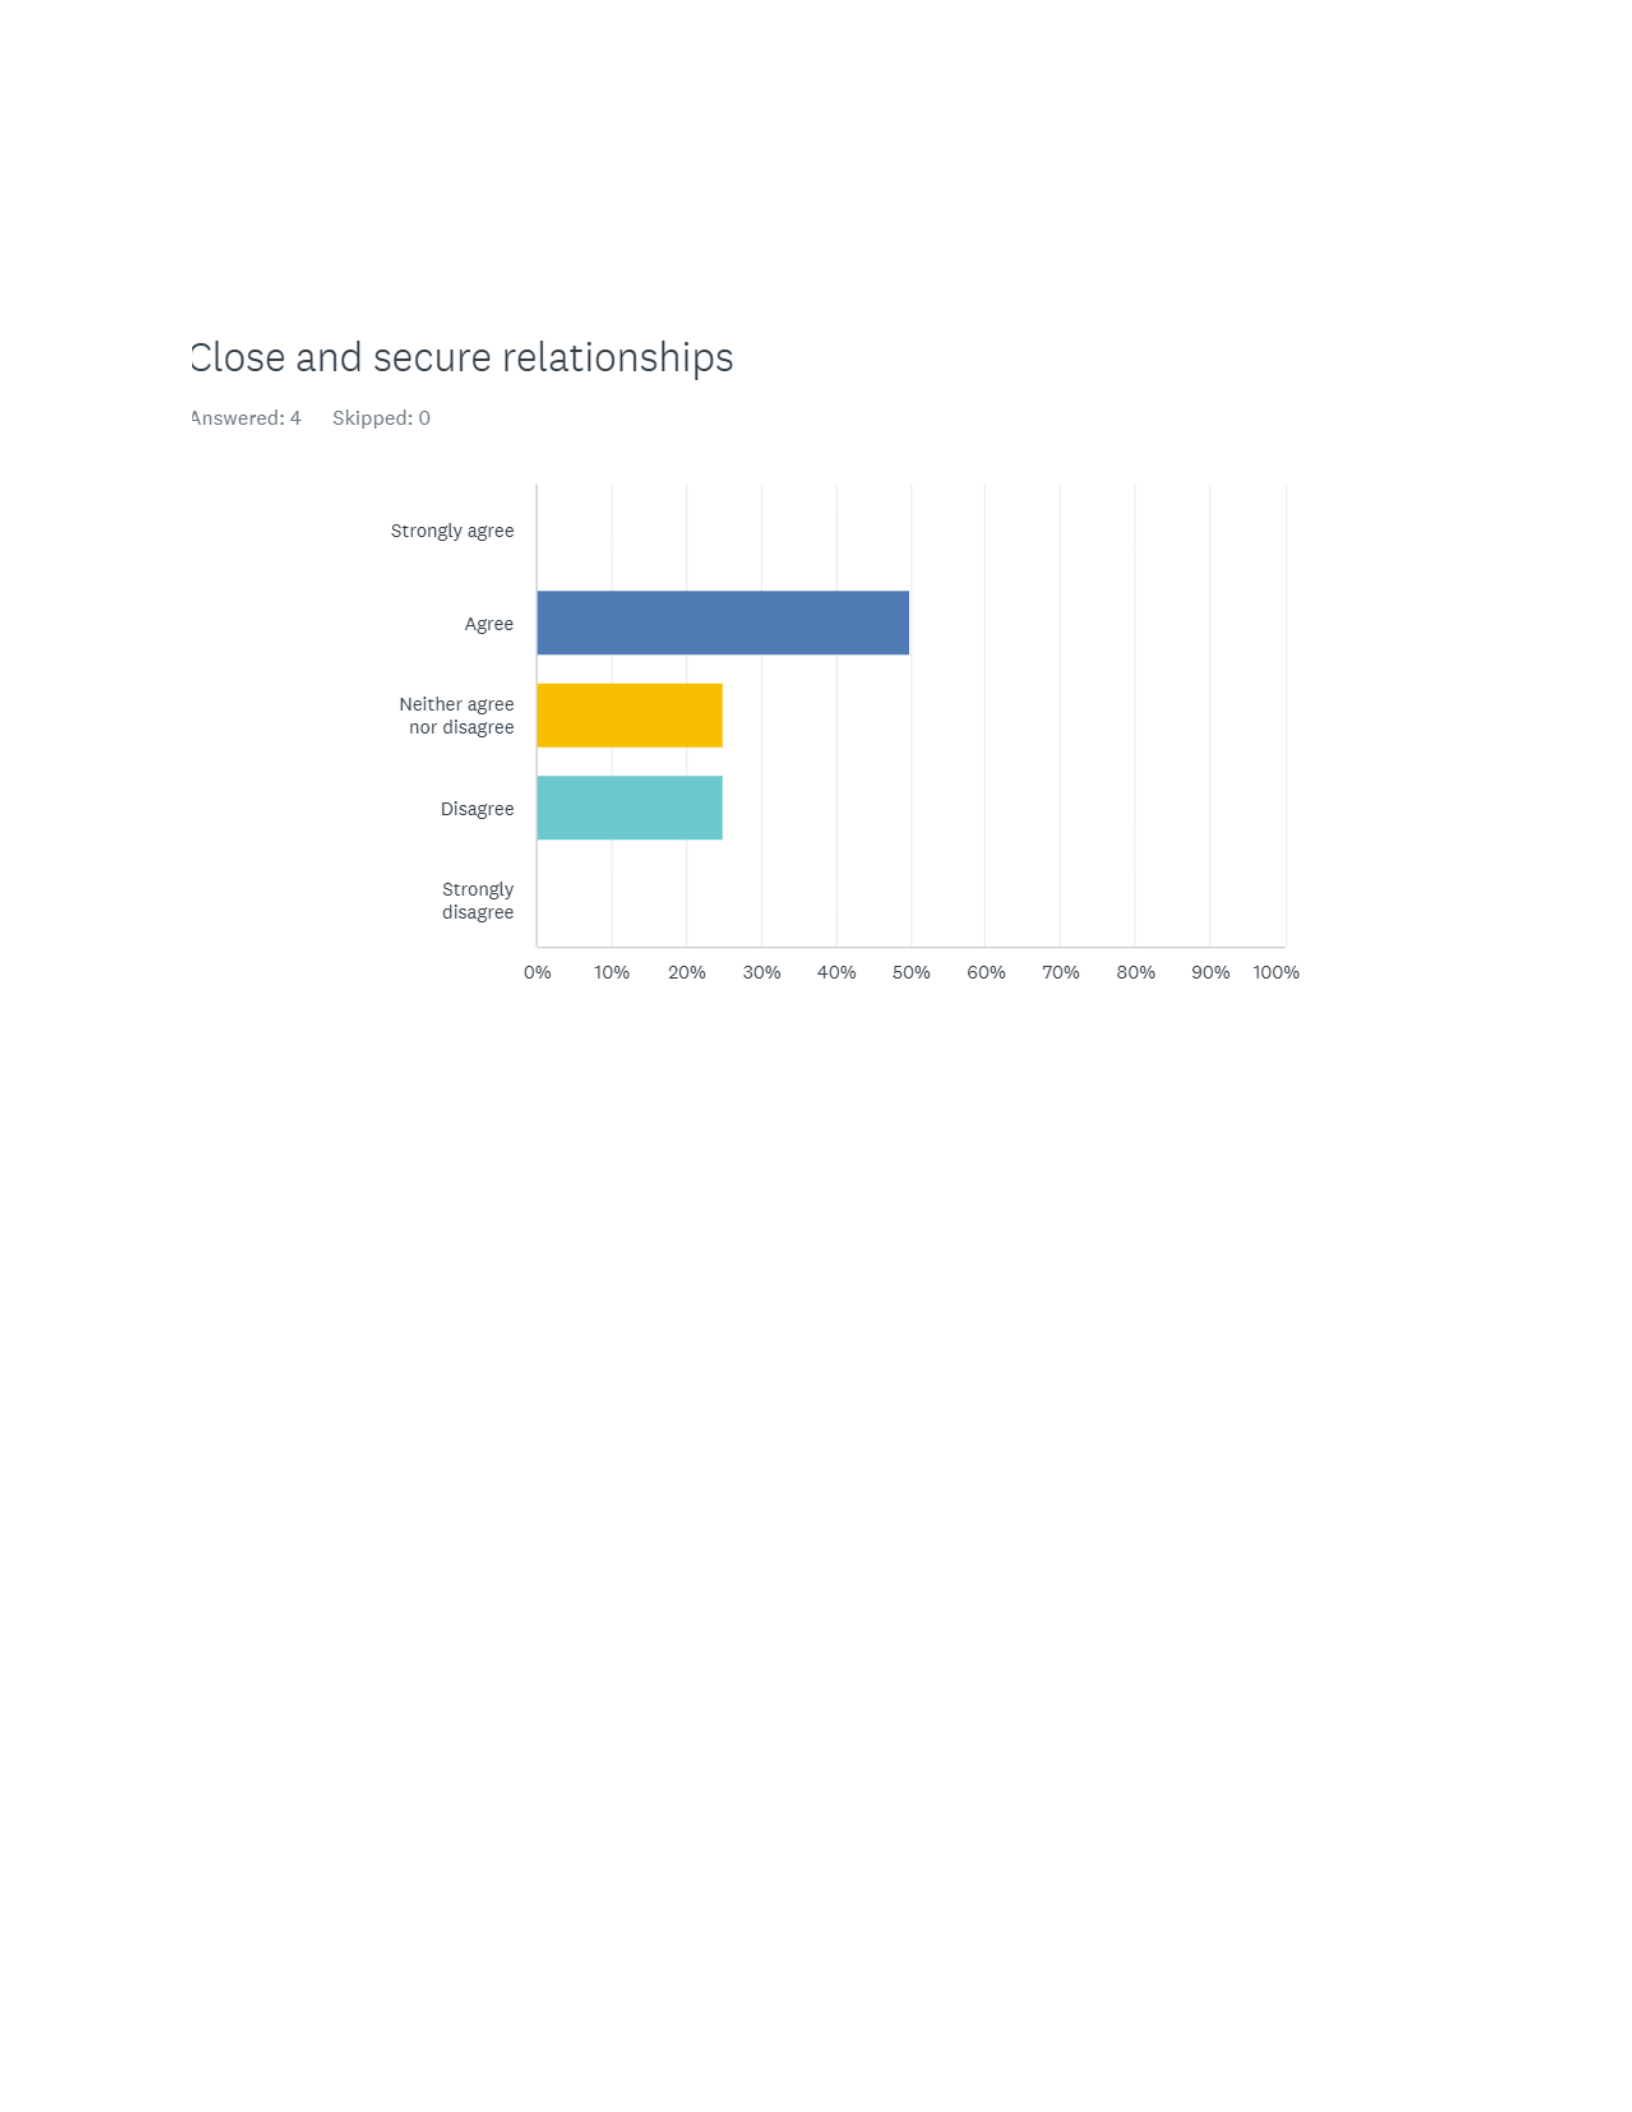
Close
and
secure
relationships
Answered:
4
Skipped:
0
strongly
agree
Agree
Neither
agree
nor
disagree
Disagree
Strongly
disagree
O%
10% 20%
30%
40%
0%
60%
10%
80%
90%
10%
214
Appendix G: Sample Code

