



CASE STUDY: AMARA 1
Case Study: Anna
Alexus Bryant
School of Behavioral Sciences, Liberty University
CASE STUDY: AMARA 2
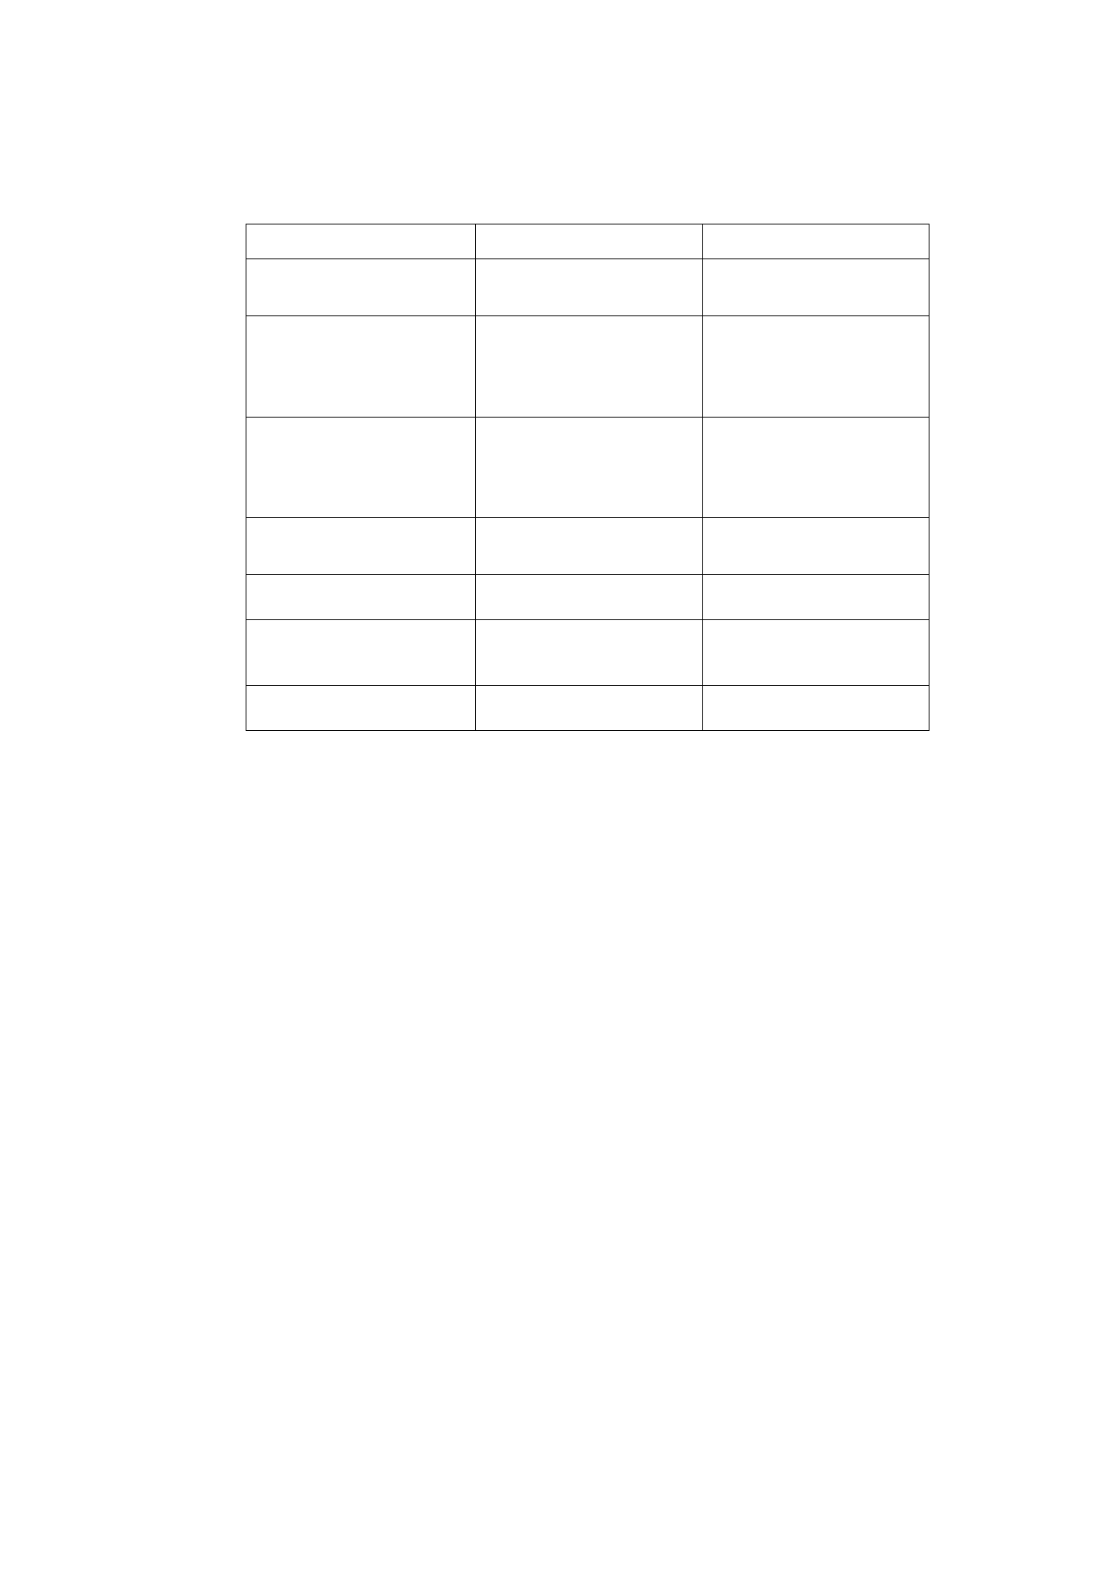
Client Concerns
Symptoms
Behaviors
Stressors
Anxiety
Anxiousness
Husband’s death and
retirement.
Trouble Sleeping
Worrying 1-2 hours a
night, waking up worrying
5-6 hours after falling
asleep.
Husband’s death, worrying
about family members,
retirement.
Worrying
Constant worrying, calling
children with high levels of
anxiety and worrying.
Husband’s death,
relationship changes with
children, taking care of her
mother.
Irritable
Snapping at her daughter,
and increased worrying.
Husband’s death,
retirement.
Tension in Body
Headaches, Shoulder, and
neck pain.
Husband’s death,
retirement.
Fatigue
Feeling tired 2-3x per
week, no motivation.
Lack of sleep due to
husband’s death, worrying,
and retirement.
Drinking
Drinking two glasses of
wine five days per week.
Retirement.
(Amara Contextual Case Study Analysis, 2021)
Assessment
Amara shows symptoms of Generalized Anxiety Disorder. For this diagnosis, the
Generalised Anxiety Disorder Assessment (GAD-7) can be used to measure Amara’s disorder.
The Generalised Anxiety Disorder Assessment is an instrument that includes seven measurable
items (Rosellini et al., 2018). The items on the assessment question the individual about their
symptoms over the last two weeks. There are several options for answers, which include ‘nearly
every day”, “more than half the days”, “several days”, and “not at all” (Rosellini et al., 2018). It
would allow me to learn the severity of Amara’s anxiety. This assessment was chosen over other
CASE STUDY: AMARA 3
assessments due to the validity, psychometric properties, research base, and simplicity of the
assessment being that it is self-administered and takes 1-2 minutes to complete.
Diagnostic Impression
The primary diagnostic impression for GAD cludes increased anxiety and worrying
about multiple topics, people, interests, or events (American Psychiatric Association, 2013). The
worry that is associated with this disorder occurs for at least six months. Individuals often state
that it is extremely hard to control. The ICD code for this disorder is F41.1. The full name of
GAD Generalized Anxiety Disorder (GAD). There are multiple diagnoses for this disorde
that may include social phobia, specific phobias, major depression, and panic disorder. The ICD-
10 code for social phobia is F40.11, the full name is social anxiety disorder. The ICD-10 code for
specific phobia is F40.2, the full name is simple phobia (isolated). The ICD-10 code for major
depression is F33.9, the full name is clinical depression. The ICD-10 code for panic disorder is
F41 he full name is panic disorder and/or anxiety disorder (American Psychiatric Association,
2013).
Signs and Symptoms
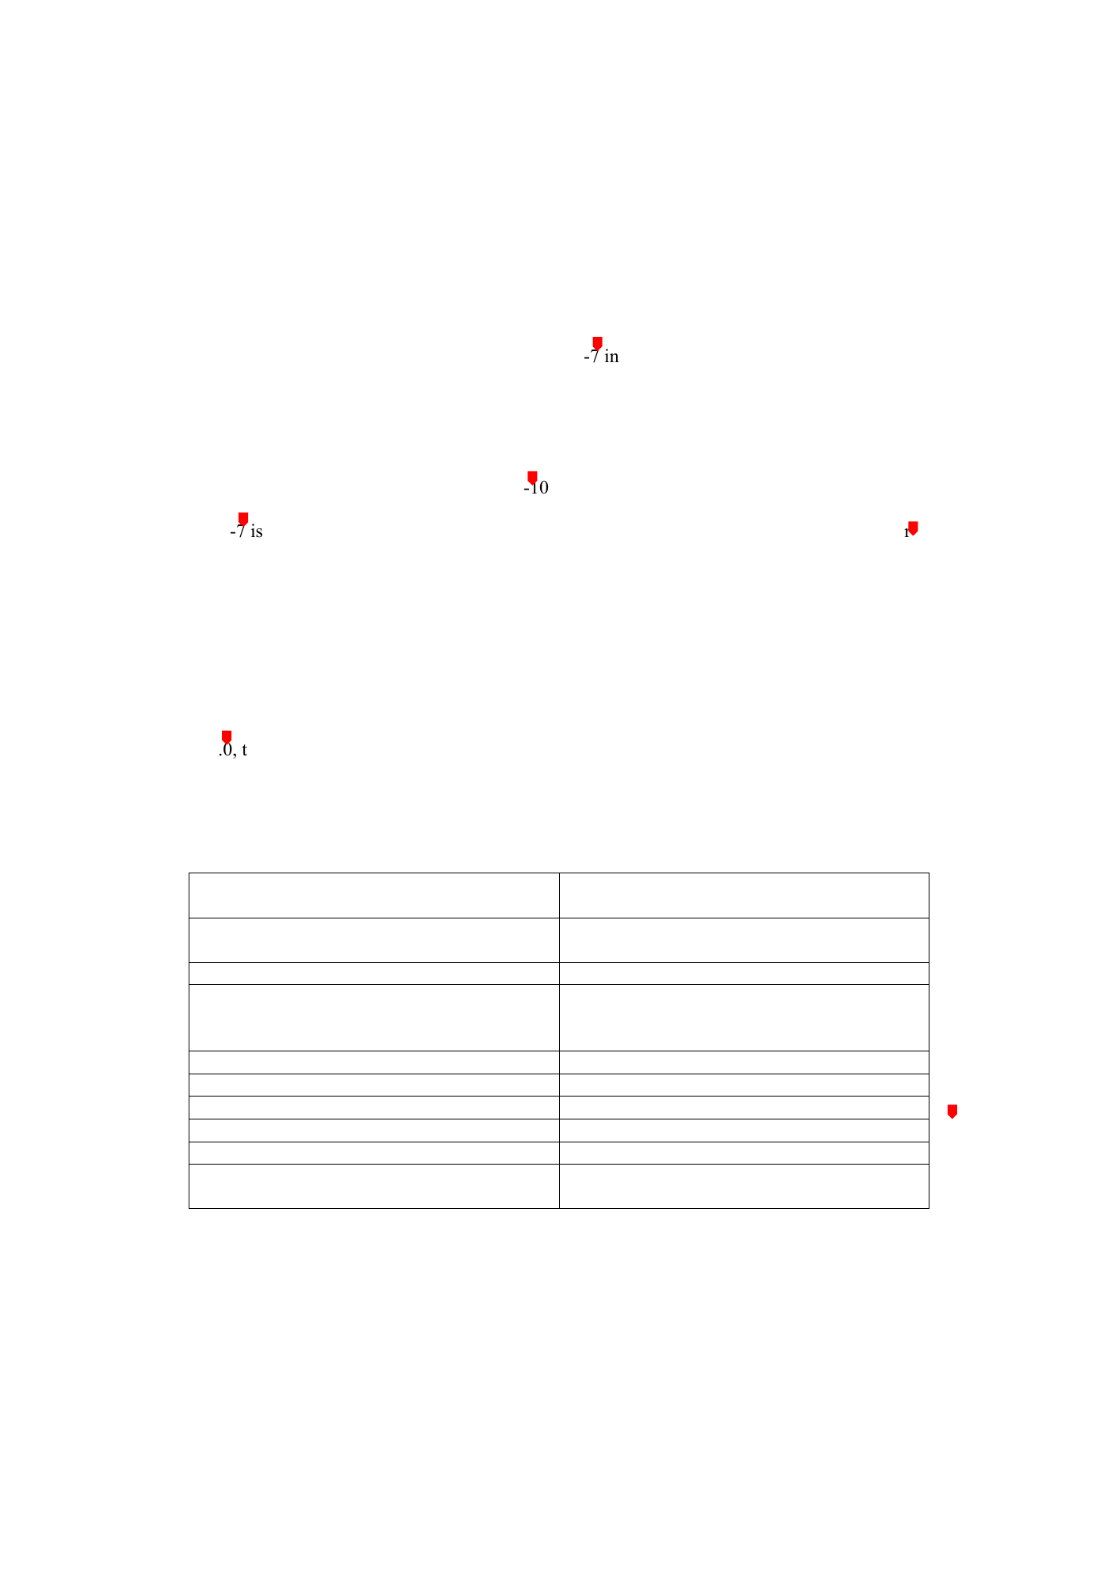
DSM-5-TR Diagnostic Criteria: Generalized
Anxiety Disorder F41.1
Client’s Signs/Reported Symptoms:
Criterion A: Excessive Anxiety
Anxiousness, Racing mind, multiple thoughts
about different things.
Criterion B: Fatigue/Sleep Disturbance
Unable to sleep past 5-6 hours, lays in bed 1-2
hours before being able to fall asleep.
Experienced fatigue for 12 months.
Criterion C: Tension in body
Headaches, and shoulder and neck pain.
Criterion D: Irritable
Snapping on family members.
Criterion E: Worrying
Uncontrollable worry, worry about things she
knows aren’t an issue.

CASE STUDY: AMARA 4
(American Psychiatric Association, 2013), (Liberty University, Case Study Amara, 2021)
Excessive drinking was also a symptom of Amara after she retired, this symptom was
considered but did not align with the DSM-5-TR
Other DSM-5-TR Conditions Considered
There were other diagnoses that were considered while going over Amara’s case
including mood disorders, eating disorders, and other cognitive disorders. The client reported
three symptoms of major depressive disorder (insomnia, fatigue, inappropriate guilt), but six or
more symptoms are needed, and the diagnosis was ruled out. Another diagnosis the writ
considered for the client was panic disorder but being that the client did not have any symptoms
of panic disorder, the diagnosis was completely ruled out.
Developmental Theories and/or Systemic Factors
Many factors influence the client’s functioning and behaviors. The client’s husband died
of cancer, which was one of the main influences on the client’s disorder and behavior. The
second factor was the client’s retirement. The client wanted to continue working after her
husband’s death not only because she enjoyed it but because it allowed her to take her mind off it
and other stressors temporarily. The changing relationship between the client and her children,
and grandchildren has also influenced her behaviors. The client had no prior mental disorders or
medical conditions prior to her physician prescribing her Paxil for her anxiety. Other factors that
are commonly associated with GAD-7 are the presence of stressors and female gender Kim et (
al., 2001). The client also experienced other complaints and psychological symptoms. The
client’s environment is associated with the behaviors and symptoms caused by this disorder. She
also cares for her 90-year-old mother who also lives with her. Although the client has always

CASE STUDY: AMARA 5
been known for being anxious, it increased extremely after her husband died and she was forced
to retire from her job. Further research needs to be discov to understand the etiology and
symptomatology of GA The client’s substance abuse also may be associated with the client’s
increased and uncontrollable worrying.
Multicultural and/or Social Justice Considerations
Family and cultural backgrounds in Asian Americans are significantly important and are
a tradition. Specific family members have a role and/or position in the family to adhere to the
things that they are expected to do (Kramer, E.J., Kwong, K., Lee, E., Chung, H., 2002). During
their lifetimes, women are particularly vulnerable to the onset of psychiatric disorders. Most
significant mood and anxiety disorders with consideration OCD, happen more every now and
again in ladies than in men. To explain this phenomenon, several biological, social, and cultural
hypotheses have been proposed. Social support has been found as a negative association when it
comes to stress and depression in Asian Americans. Social support has changed the effect of
stressors on mental and physical health among diverse Asian American groups (Choi, 1997; Gee
et al., 2006). Rather than Western cultures, a collectivist direction might upset individual issues
inspired by a paranoid fear of troubling others, disturbing group peace, or losing face (B.S.K.
Kim, Atkinson, and Umemoto, 2001; H. S. Kim et al., 2006). The client has not received social
support from family and friends due to her excessive worrying and inability to decrease these
symptoms around them. Studies have found that support is linked to well-being, support is linked
to improved health while strain is linked to decreased mental health (Revenson et al., 1987). It
was also found that taking care of a family member can cause strain in personal relationships due
to the feeling of obligation to their position or role in the family. The client is Hindu which can

CASE STUDY: AMARA 6
also have a major influence on the way the client receives treatment. Looking into holistic
treatments for the client may be beneficial.
Treatment Recommendations
Key Issues for Treatment
Worrying & Anxiousness (Retirement and Husband’s Death)
Trouble Sleeping & Fatigue
Lack of support from family and friends
The client is still having symptoms and is willing to accept treatment. These three
issues/symptoms are key components that have influenced the client and may have increased the
severity of the client’s disorder. Different techniques in treatment may be used to help the client.
There are multiple ways to decrease the client’s symptoms and issues which can include therapy,
mindfulness therapy, and other ways to initiate relaxation.
Recommendations for Individual Counseling
Cognitive Behavioral Therapy has been shown to be reliable and effective for people
with GAD and other forms of anxiety, according to Evans (2016). Circling back to care-based
mental social treatment is ideal because of the high relapse rates and low achievement rate in
treatment (Evans, 2016). Family treatment centers around further developing correspondence
between moms, youngsters, and grandkids (Goldenburg et al., 2017). If the Paxil that was
recommended doesn't work for the client, her physician will have to up the dosage or go through
different trials of different medications (Amara Contextual analysis, 2021). Being that the client
practices Hinduism, there are different practices that can be used for treatment. Faith healing,
psychotherapy, Unani medicine, meditations, and practices of mindfulness are all techniques that

CASE STUDY: AMARA 7
could be practiced being that the client requested to integrate her religion into counseling. The
client's family is also being affected by the client’s worries. Integrating family/group therapy for
the family can help build the relationship back with her children and grandchildren. While
conducting research, it was found that when practicing mindf ss, this method focuses on the
present instead of the past, being deliberately mindful of what's going on inside and outside, with
practically no response. This method prompts self-reflection and physical responses rather than
automatic responses (Sharma, M., Mao, A., Sudhir, P., 2012). Mindfulness seeks to improve
knowledge and decrease one's suffering by zeroing in on the current moment. Mindfulness
prompts separating oneself from the outside world and turns the focal point of the individual
internally, breaking the typical patterns of answering when anxious. What's more, it additionally
incorporates relaxation strategies, which are viable for lessening anxiety (Sharma, M., Mao, A.,
Sudhir, P., 2012).
Being that the client is already receiving medication and has just begun, medication would
not be recommended. The client is still in her first few weeks of starting the medication. Over
time, the client and physician will focus on the client’s symptoms with the medication to
determine if the dosage needs to be increased or her medication may need to be changed. The
client’s physician prescribed the client Paxil. Paxil (Paroxetine) is a selective serotonin reuptake
inhibitor (SSRI) (Shrestha, P., Fariba, K.A., Abdijadid, S, 2023). It is used to treat not only
GAD-7 but other disorders including OCD, social anxiety disorder, major depressive disorder,
and premenstrual dysphoric disorder. This medication is taken orally and based on the client's
symptoms and tolerance to the amount given. Adults usually start off with 20mg by mouth daily
and can be subject to increase to 60mg per week depending on the severity of the client’s anxiety
(Germann, D., Ma, G., Han, F., Tikhomirova, A, 2013). There are several side effects that the

CASE STUDY: AMARA 8
client may experience like sweating, sleep disturbance, loss of appetite, dry mouth, drowsiness,
etc. Being that these side effects are similar to the symptoms of the disorder could be the reason
the client is not seeing a significant change in her symptoms (Bahar, M. A., Wang, Y., Bos, J. H.,
Wilffert, B., Hak, E., 2018).
Specific Considerations
Cultural background plays a significant role in this case due to the client’s religion and
race. Asian Americans and their family dynamic is a huge part of their culture. It is usually
common that Asian Americans do not tend to seek professional or counseling help when
experiencing mental health disorders. Their cultural beliefs often hinder or result in a lack of
treatment because they would rather avoid being seen as abnormal or unable to take charge of
their role. While additional information would be needed, the counselor may want to know the
levels of dependence the client has being that the medication could be abus The counselor
may also need to know about any other over-the-counter medications the client may be taking
because some can intensify anxiety symptoms. The client’s family and religious values may
conflict with treatment being that the level of dependence of the client and her role could be
associated with the stressors. The counselor should be aware of the client's culture, ethnicity, and
background when working with a client with any disorder. This permits the client to feel good
about treatment. A culturally aware therapist focuses on how they might interpret the client's
belief system. Therapists can accommodate and respect minority opinions, values, and attitudes
by incorporating cultural competency and cultural sensitivity into mental health services (Lyons,
H., 2020

CASE STUDY: AMARA 9
References
American Psychiatric Association. (2013). Diagnostic and statistical manual of mental disorders
(5th ed.). American Psychiatric Association Publishing.
Bahar, M. A., Wang, Y., Bos, J.H.J., Wilffert, B., Hak, E. Discontinuation and dose adjustment
of metoprolol after metoprolol-paroxetine/fluoxetine co-prescription in Dutch elderly.
Pharmacoepidemiology Drug Saf. 2018 Jun;27(6):621-629.
Choi, G., Acculturative stress, social support, and depression in Korean American families,
Journal of Family Social Work, 1997, vol. 2 (pg. 81-97).
Evans, S. (2016). Mindfulness-based cognitive therapy for generalized anxiety disorder.
Springer.
Germann, D., Ma, G., Han, F., Tikhomirova, A. Paroxetine hydrochloride. Profiles Drug Subst
Excip Relat Methodol. 2013;38:367-406.
ps://doi.org/10.1177/0011000001294006.
Kim, B. S. K., Atkinson, D. R., & Umemoto, D. (2001). Asian Cultural Values and the
Counseling Process: Current Knowledge and Directions for Future Research. Counseling
Psychologist, 29, 570-603.
Kramer, E.J., Kwong, K., Lee, E., Chung, H., Cultural factors influencing the mental health of
Asian Americans. West J Med. 2002 Sep;176(4):227-31. PMID: 12208826; PMCID:
PMC1071736.
Liberty University. (2021). CEFS546 Amara Case Study [Course Article]. Canvas.
https://canvas.liberty.edu.

CASE STUDY: AMARA 10
Munir, S., Takov, V., Generalized Anxiety Disorder. [Updated 2022 Oct 17]. In: StatPearls
[Internet]. Treasure Island (FL): StatPearls Publishing; 2023 Jan-. Available from:
https://www.ncbi.nlm.nih.gov/books/NBK441870/.
Revenson, T. A., Schiaffino, K. M., Majerovitz, S., D., Gibofsky, A. Social support as a double-
edged sword: The relation of positive and problematic support to depression among
rheumatoid arthritis patients, Social Science and Medicine, 1991, vol. 33 (pg. 807-813).
Rosellini, A.J., Bourgeois, M.L., Correa, J., Tung, E.S., Goncharenko, S., Brown, T.A., Anxious
distress in depressed outpatients: Prevalence, comorbidity, and incremental validity. J
Psychiatr Res. 2018 Aug;103:54-60.
Sharma M., Mao A., Sudhir P. Mindfulness-based cognitive behavior therapy in patients with
anxiety disorders: a case series. Indian J Psychol Medicine. 2012;34(3):263–269.
Shrestha, P., Fariba, K.A., Abdijadid, S. Paroxetine. [Updated 2023 Jul 17]. In: StatPearls
[Internet]. Treasure Island (FL): StatPearls Publishing; 2023 Jan-. Available from:
https://www.ncbi.nlm.nih.gov/books/NBK526022/.

