




BENCHMARK CASE PRESENTATION 2
Benchmark Case Presentation
Basic Case Summary
Identifying Information
As of January 20, 2023, Alex Mitchell engaged in his initial assessment. He is a 28-year-
old male and currently serves as a marketing specialist. Alex is not currently enrolled in any
academic program, as he is focused on his professional career currently. His ethnic background
is European, and his race is white. In the realm of marital status, he identifies as single. This
comprehensive snapshot of Alex’s demographics provides a foundation for understanding his
case.
Reason for Referral/Presenting Concern
Alex sought counseling due to a recent increase in anxiety and distress. He reported
persistent intrusive thoughts about contamination and an overwhelming urge to perform
ritualistic behaviors, such as frequent handwashing. His symptoms are affecting various aspects
of his life, including his occupational tasks. His desire to repetitively perform behaviors
negatively affects his work efficiency. His habits not only affect his productivity, but he also has
challenges meeting important deadlines at work. He is not able to concentrate or focus on the
task at hand since his mind is preoccupied with his ritual behaviors.
Alex stated, “I used to be so spontaneous, and now anything outside of my routine scares
me, and I feel like I will not be able to enjoy activities outside of my routine. Also, being in the
outside world means that I am susceptive to disease and illness. No one can convince me that my
fears are not valid, as the outbreak of COVID-19 was so detrimental. Being without germs is the
only thing that makes me feel safe. All I can think about is the thousands of microorganisms
crawling around my hands and body at all times of the day. I am afraid of what others will think

BENCHMARK CASE PRESENTATION 3
if they see me spending two hours in the bathroom washing my hands or counting random things
like the number of tiles on the floor to distract me. I think people will make fun of me for how I
act because it has happened before.” His avoidance of social activities leads to feelings of
isolation and prohibits developing new relationships. Alex suggests that his mother deals with
similar problems and that that is why his father left her. He said “She never went to any of my
father’s social events, and after some time, my father found someone that fit his mold. Also, it is
not my fault that I want to be at home all the time since my mother was the same way.” Seeing
his mother’s isolating behaviors has normalized his social avoidance.
History
Family and Home/Religious Background
Alex was raised in a supportive environment by his parents, Emily (56) and Michael (59),
along with a younger sister, Olivia (25). His parents divorced eight years ago when he was 20.
They still have an amicable relationship, but his father quickly remarried a year after the divorce.
Alex describes his family as close-knit growing up, and that there were no critical family
incidents in his childhood.
Educational History
Alex completed a bachelor’s degree in business administration with a specialty in
marketing and decided not to pursue higher education. He was offered an above-entry-level
marketing job out of college and decided to focus on his professional career. He talks about
potentially going back for a master’s degree in business, but his distress has impacted his ability
to focus on his educational goals.
Mental Health

BENCHMARK CASE PRESENTATION 4
Alex has a history of anxiety, with recent signs and symptoms including intrusive
thoughts and heightened distress. His anxiety symptoms became noticeable approximately five
years ago during a period of increased work pressure and responsibilities. Currently, via mental
health test results, including the DSM-5 cross-cutting symptom measure, Alex indicates a
significant level of obsessive-compulsive symptoms.
Client’s Physical Health
Alex reports no significant physical health issues. He is also not currently on any medications.
He was never given medication for his anxiety symptoms in the past either.
Occupational History
Alex has been working as a marketing specialist since he graduated college 5 years ago.
He almost moved over to a sales position last year within the same company, but he did not feel
confident enough to be socializing with unfamiliar individuals. Recent occupational functioning
has been affected by the need to repeat tasks multiple times a day.
Sexual Adjustment
Alex reports no significant problems or disturbances in sexual functioning. He has had a
few partners over the last five years but is not currently sexually active.
Substance Use History
He does not engage in alcohol or drug use currently. Alex reports having a few alcoholic
drinks during social events during his college years, but that he does not enjoy the feeling of
intoxication. He claims that he has not had any alcoholic drinks in over five years and has never
taken any other non-prescription substance.
Spiritual Assessment

BENCHMARK CASE PRESENTATION 5
Religious practices were minimal in the household. Alex does believe there is a higher
power but does not associate with any specific religion. His mother grew up Christian but
stopped actively going to church once she was 18 and out of the house. Michael, his father, also
believes there is a higher power, but there were never any concrete discussions in the family
about religious beliefs that Alex can remember.
Cultural/ Social Justice Factors
Alex does not report any factors such as acculturation or discrimination that have
personally impacted him.
Barriers to Treatment/Success
Perfectionistic tendencies and the fear of judgment from others may impact treatment
success. Alex is in a contemplative state of change, so it is hard to determine without a doubt if
his symptoms can be treated.
Mental Status Exam
Alex presents with a very neat and clean appearance. He is alert and his speech is clear,
but he struggles to make consistent eye contact, especially at the beginning of the assessment.
His thought processes are coherent, and he can comprehend the interview questions. He
continuously touches his hair and taps his foot during most of the session. He switches from
tapping his right foot to his left foot about every minute or so. He seems to get distracted when
he switches which foot he is tapping as if he is keeping track of his taps.
He uses a wide range of vocabulary and uses full sentences, demonstrating his intellectual
ability. He appears to be nervous and closely watches my facial expressions after he answers
questions. However, his nature is non-threatening, and he has a soft tone of voice. He does not
report any suicidal or homicidal ideation.
BENCHMARK CASE PRESENTATION 6
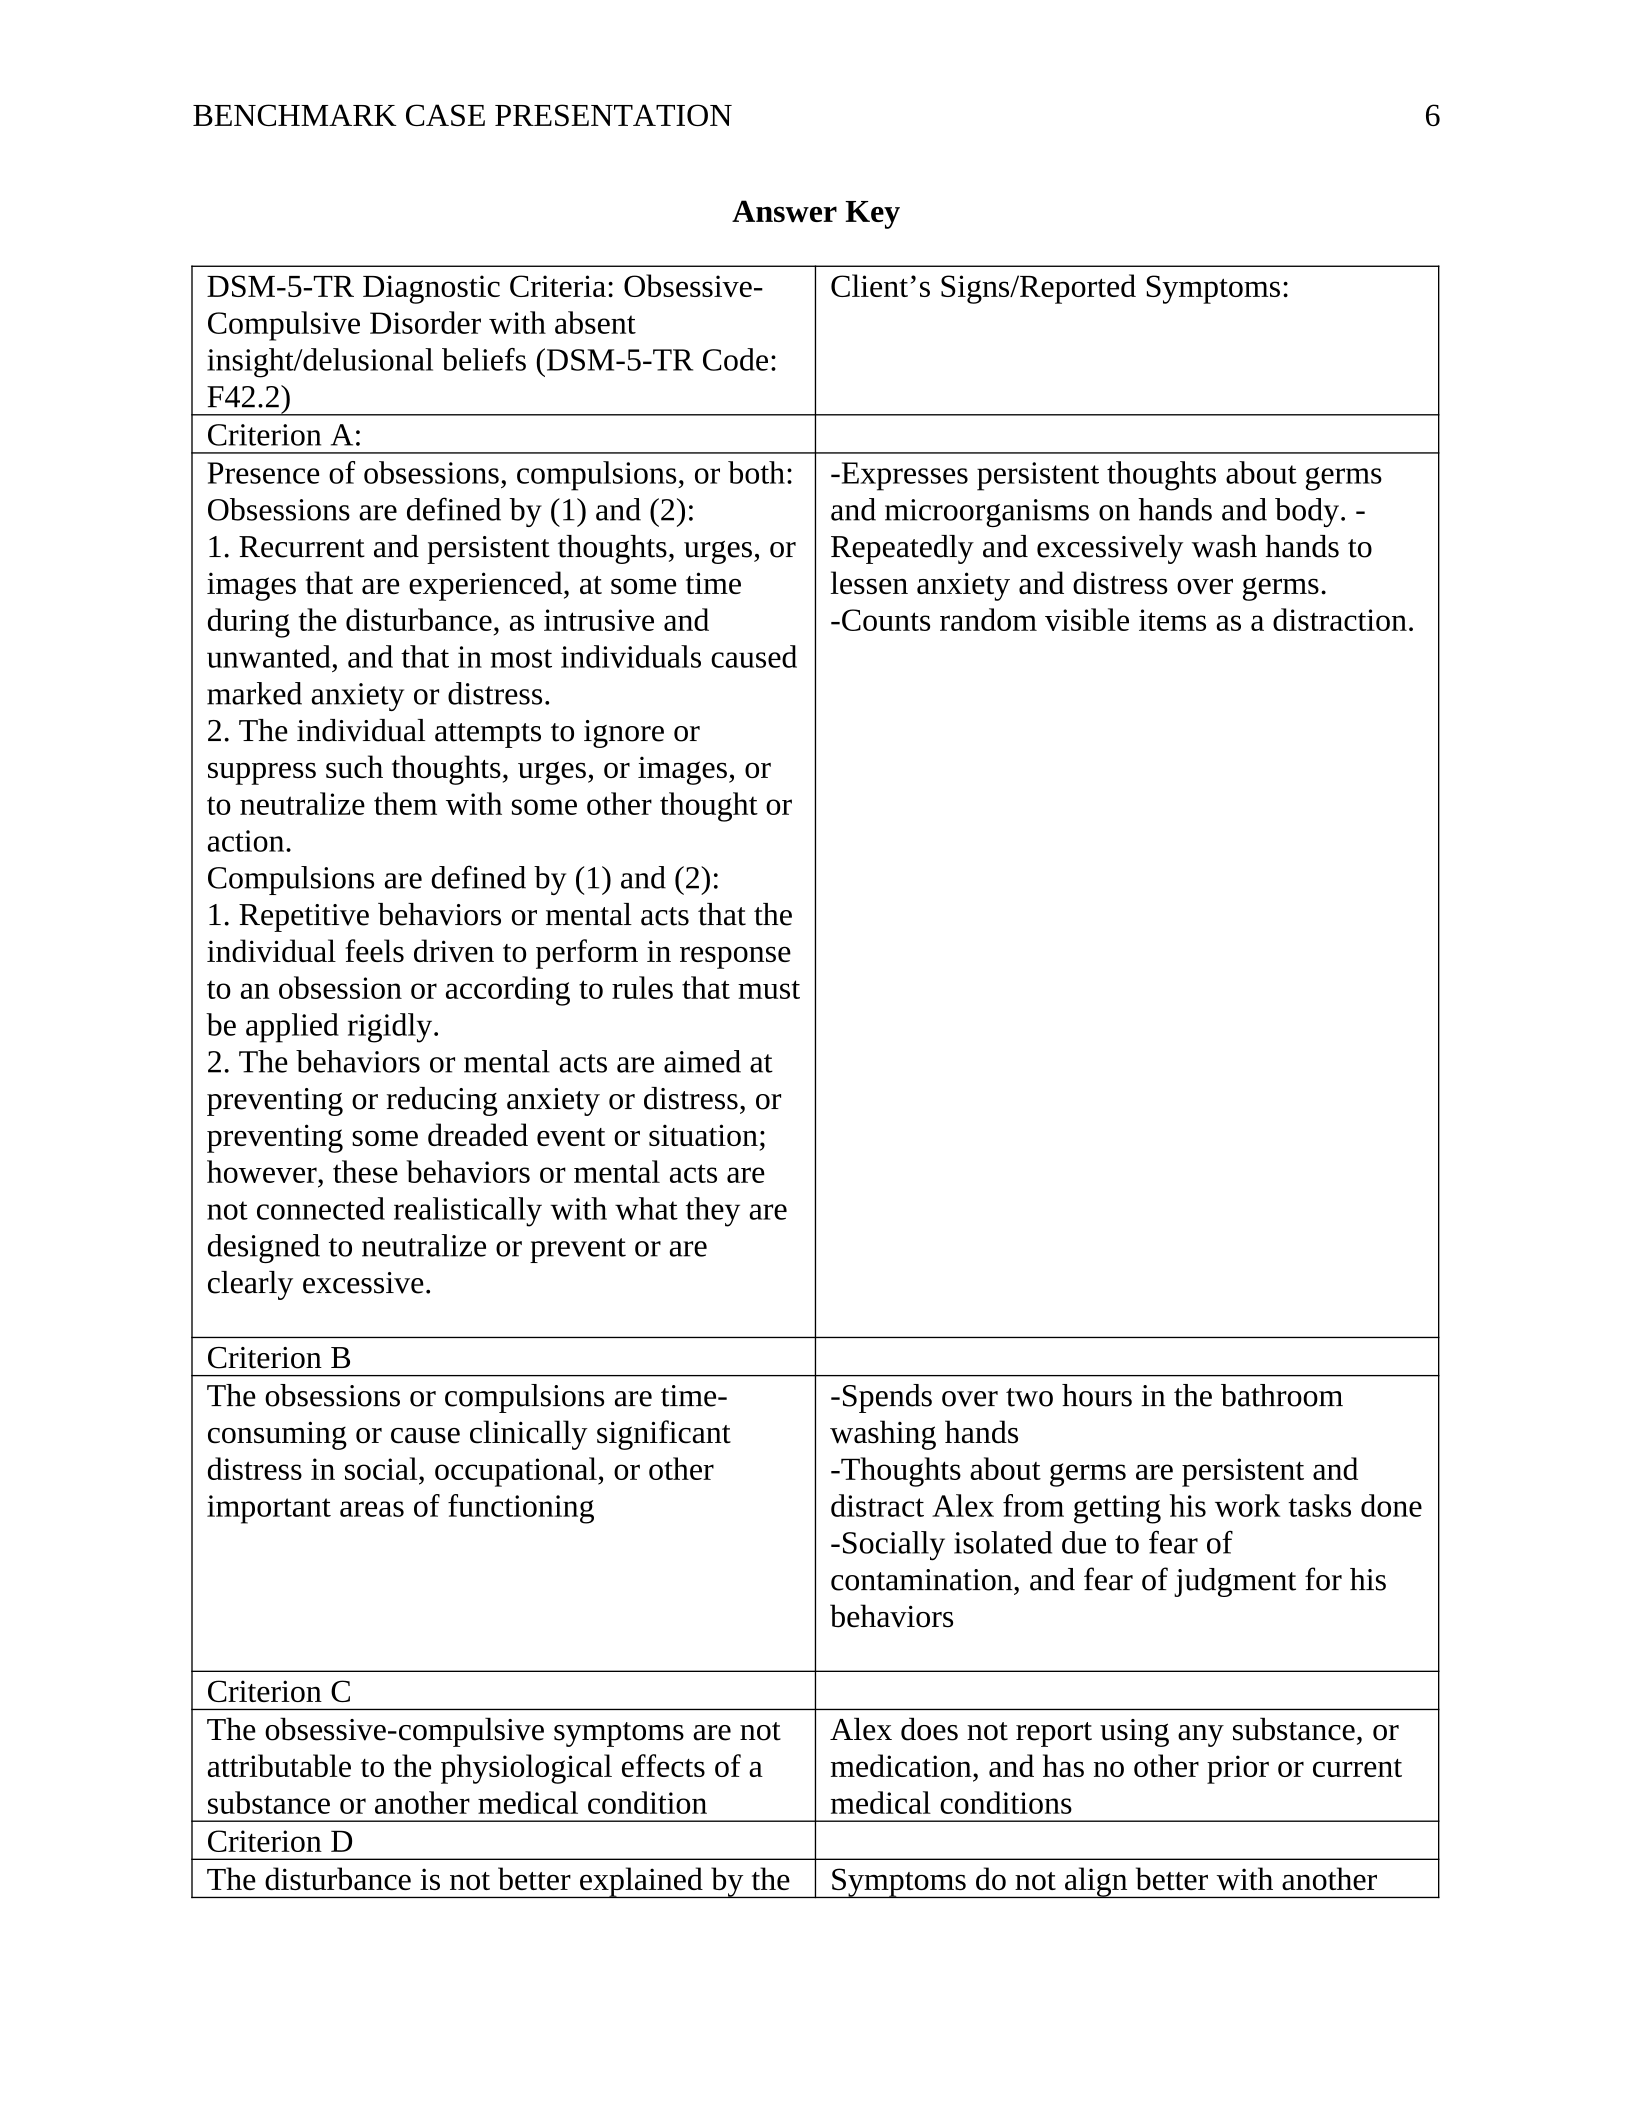
Answer Key
DSM-5-TR Diagnostic Criteria: Obsessive-
Compulsive Disorder with absent
insight/delusional beliefs (DSM-5-TR Code:
F42.2)
Client’s Signs/Reported Symptoms:
Criterion A:
Presence of obsessions, compulsions, or both:
Obsessions are defined by (1) and (2):
1. Recurrent and persistent thoughts, urges, or
images that are experienced, at some time
during the disturbance, as intrusive and
unwanted, and that in most individuals caused
marked anxiety or distress.
2. The individual attempts to ignore or
suppress such thoughts, urges, or images, or
to neutralize them with some other thought or
action.
Compulsions are defined by (1) and (2):
1. Repetitive behaviors or mental acts that the
individual feels driven to perform in response
to an obsession or according to rules that must
be applied rigidly.
2. The behaviors or mental acts are aimed at
preventing or reducing anxiety or distress, or
preventing some dreaded event or situation;
however, these behaviors or mental acts are
not connected realistically with what they are
designed to neutralize or prevent or are
clearly excessive.
-Expresses persistent thoughts about germs
and microorganisms on hands and body. -
Repeatedly and excessively wash hands to
lessen anxiety and distress over germs.
-Counts random visible items as a distraction.
Criterion B
The obsessions or compulsions are time-
consuming or cause clinically significant
distress in social, occupational, or other
important areas of functioning
-Spends over two hours in the bathroom
washing hands
-Thoughts about germs are persistent and
distract Alex from getting his work tasks done
-Socially isolated due to fear of
contamination, and fear of judgment for his
behaviors
Criterion C
The obsessive-compulsive symptoms are not
attributable to the physiological effects of a
substance or another medical condition
Alex does not report using any substance, or
medication, and has no other prior or current
medical conditions
Criterion D
The disturbance is not better explained by the Symptoms do not align better with another

BENCHMARK CASE PRESENTATION 7
symptoms of another mental disorder. mental condition
Treatment Recommendations
The prioritization of treatment is based on the effects intrusive thoughts and compulsive
behaviors have on Alex’s well-being and overall functioning. One treatment I would recommend
is cognitive behavioral therapy (CBT), to address his maladaptive thought patterns. The other
treatment I would suggest is mindfulness-based cognitive therapy (MBCT) to enhance his
awareness of his thoughts without feeling shame, judgment, or guilt.
Treatment Recommendation 1
Cognitive behavioral therapy (CBT) is an effective approach for addressing the
overestimation of a threat and perfectionist tendencies (Morris & Nightingale, 2014). In Alex’s
case, he perceives germs to be a threat to the point where he cannot think about anything other
than contamination. While it is expected that someone would not want to get sick, the normal
expectation is that they can still function in their daily lives without ruminating thoughts of
illness. CBT can challenge the importance Alex places on complete cleanliness and the
overestimation of sickness regarding germ exposure.
Treatment Recommendation 2
Alex experiences various symptoms that interfere with his daily functioning. MBCT
would directly address the reactive thoughts and feelings that arise from the disturbance (Key et
al. 2017). Oftentimes, individuals with OCD feel as though their thoughts are never-ending and
that they have no control over their thought patterns. However, mindfulness interventions help
the individual detach from these harmful thoughts and take on an observant posture instead. By
disentangling their identity from their thoughts, their negative feelings and anxiety lessen.
Medication Considerations

BENCHMARK CASE PRESENTATION 8
It is important to evaluate Alex for medication evaluation, specifically focusing on
alleviating the obsessive-compulsive symptoms. The use of selective serotonin reuptake
inhibitors (SSRIs) is known to be more effective when paired with cognitive behavioral therapy
(Kahn, 2019). SSRIs are a class of antidepressants that aim to increase mood regulation and
maladaptive thoughts. It often takes several weeks before the SSRIs take full effect, so it is
important to give the medication time to work if that is the route chosen for the client.
References
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders
(5th ed., text rev.). https://doi.org/10.1176/appi.book.s9780890425787

BENCHMARK CASE PRESENTATION 9
Khan, A. M. (2019). The effectiveness of selective serotonin reuptake inhibitors (SSRI) for
treatment of obsessive compulsive disorder (OCD) in adolescents and children: A
systematic review and meta-analysis. Journal of Affective Disorders, 254, 154-155.
https://doi.org/10.1016/j.jad.2018.10.348
Key, B. L., Rowa, K., Bieling, P., McCabe, R., & Pawluk, E. J. (2017). Mindfulness-based
cognitive therapy as an augmentation treatment for obsessive–compulsive disorder.
Clinical Psychology & Psychotherapy, 24(5), 1109-1120.
https://doi.org/10.1002/cpp.2076
Morris, L., & Nightingale, J. (2014). CBT for OCD: habituation or cognitive shift? The
Cognitive Behaviour Therapist, 7. https://doi.org/10.1017/s1754470x14000063
Powered by TCPDF (www.tcpdf.org)

