


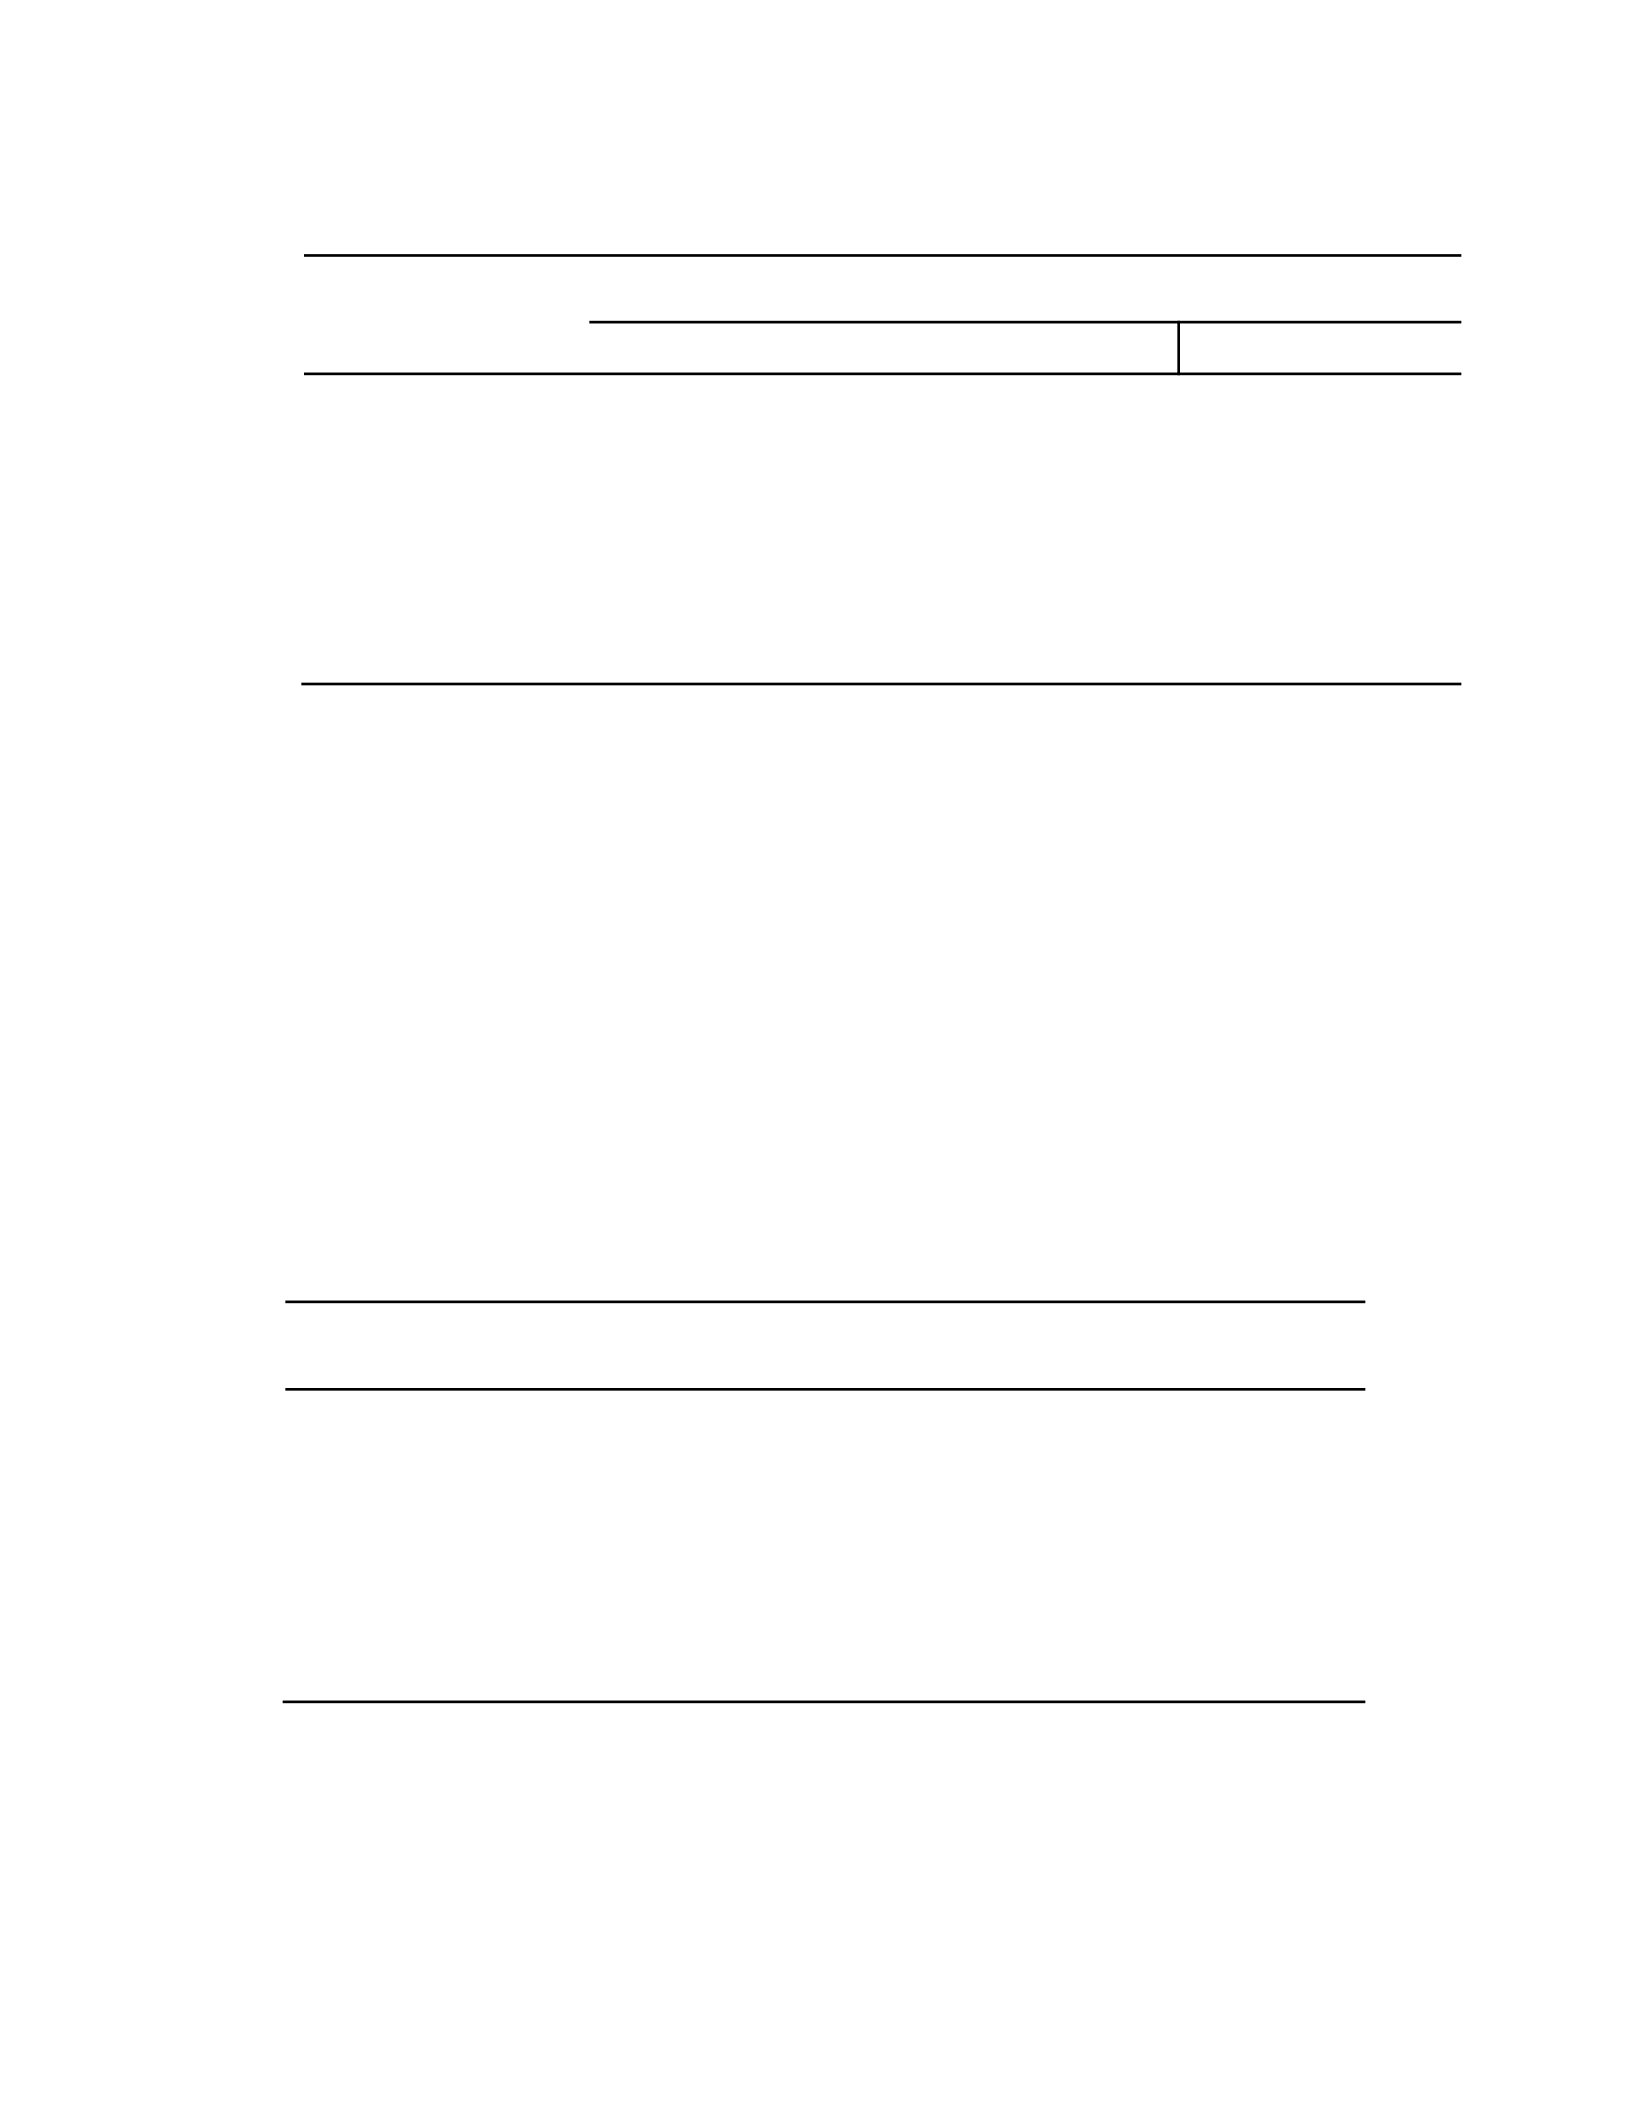
HIV test and meals needed per day
What number of meals do you normally eat per day
Total
one two Three Four > four
Ever tested for HIV
11 64
218
16 20
329
Percentage 3.0% 17.7% 60.4% 4.4% 5.5% 91.1%
Never tested for HIV 0
7
22
2 1
32
Percentage 0.0% 1.9% 6.1% 0.6% 0.3% 8.9%
Total
11 71
240
18 21
361
Percentage 3.0% 19.7% 66.5% 5.0% 5.8% 100.0%
Table shows that those who have tested for HIV have a clearer knowledge of how many
meals people living with HIV are supposed to take as compared to those who have never
tested for HIV. A chi-square test of independence was used compare the frequency of
cereals that are rich source of iron between those who have been tested HIV and those
who have not as indicated in the table
Table Chi-Square Tests
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square 1.734a
4
.785
Likelihood Ratio 2.776
4
.596
Linear-by-Linear Association
.000
1
.986
N of Valid Cases 361
From table 4.28, it is clear that participants who have ever tested for HIV have
insignificantly related the number of meals consumed in a day. (χ2 (2) = 1.734, p >0.05).
Also, the researcher sought to find out whether the level of education was a factor in the
knowledge about locally available vegetables rich in iron. Table shows the results.
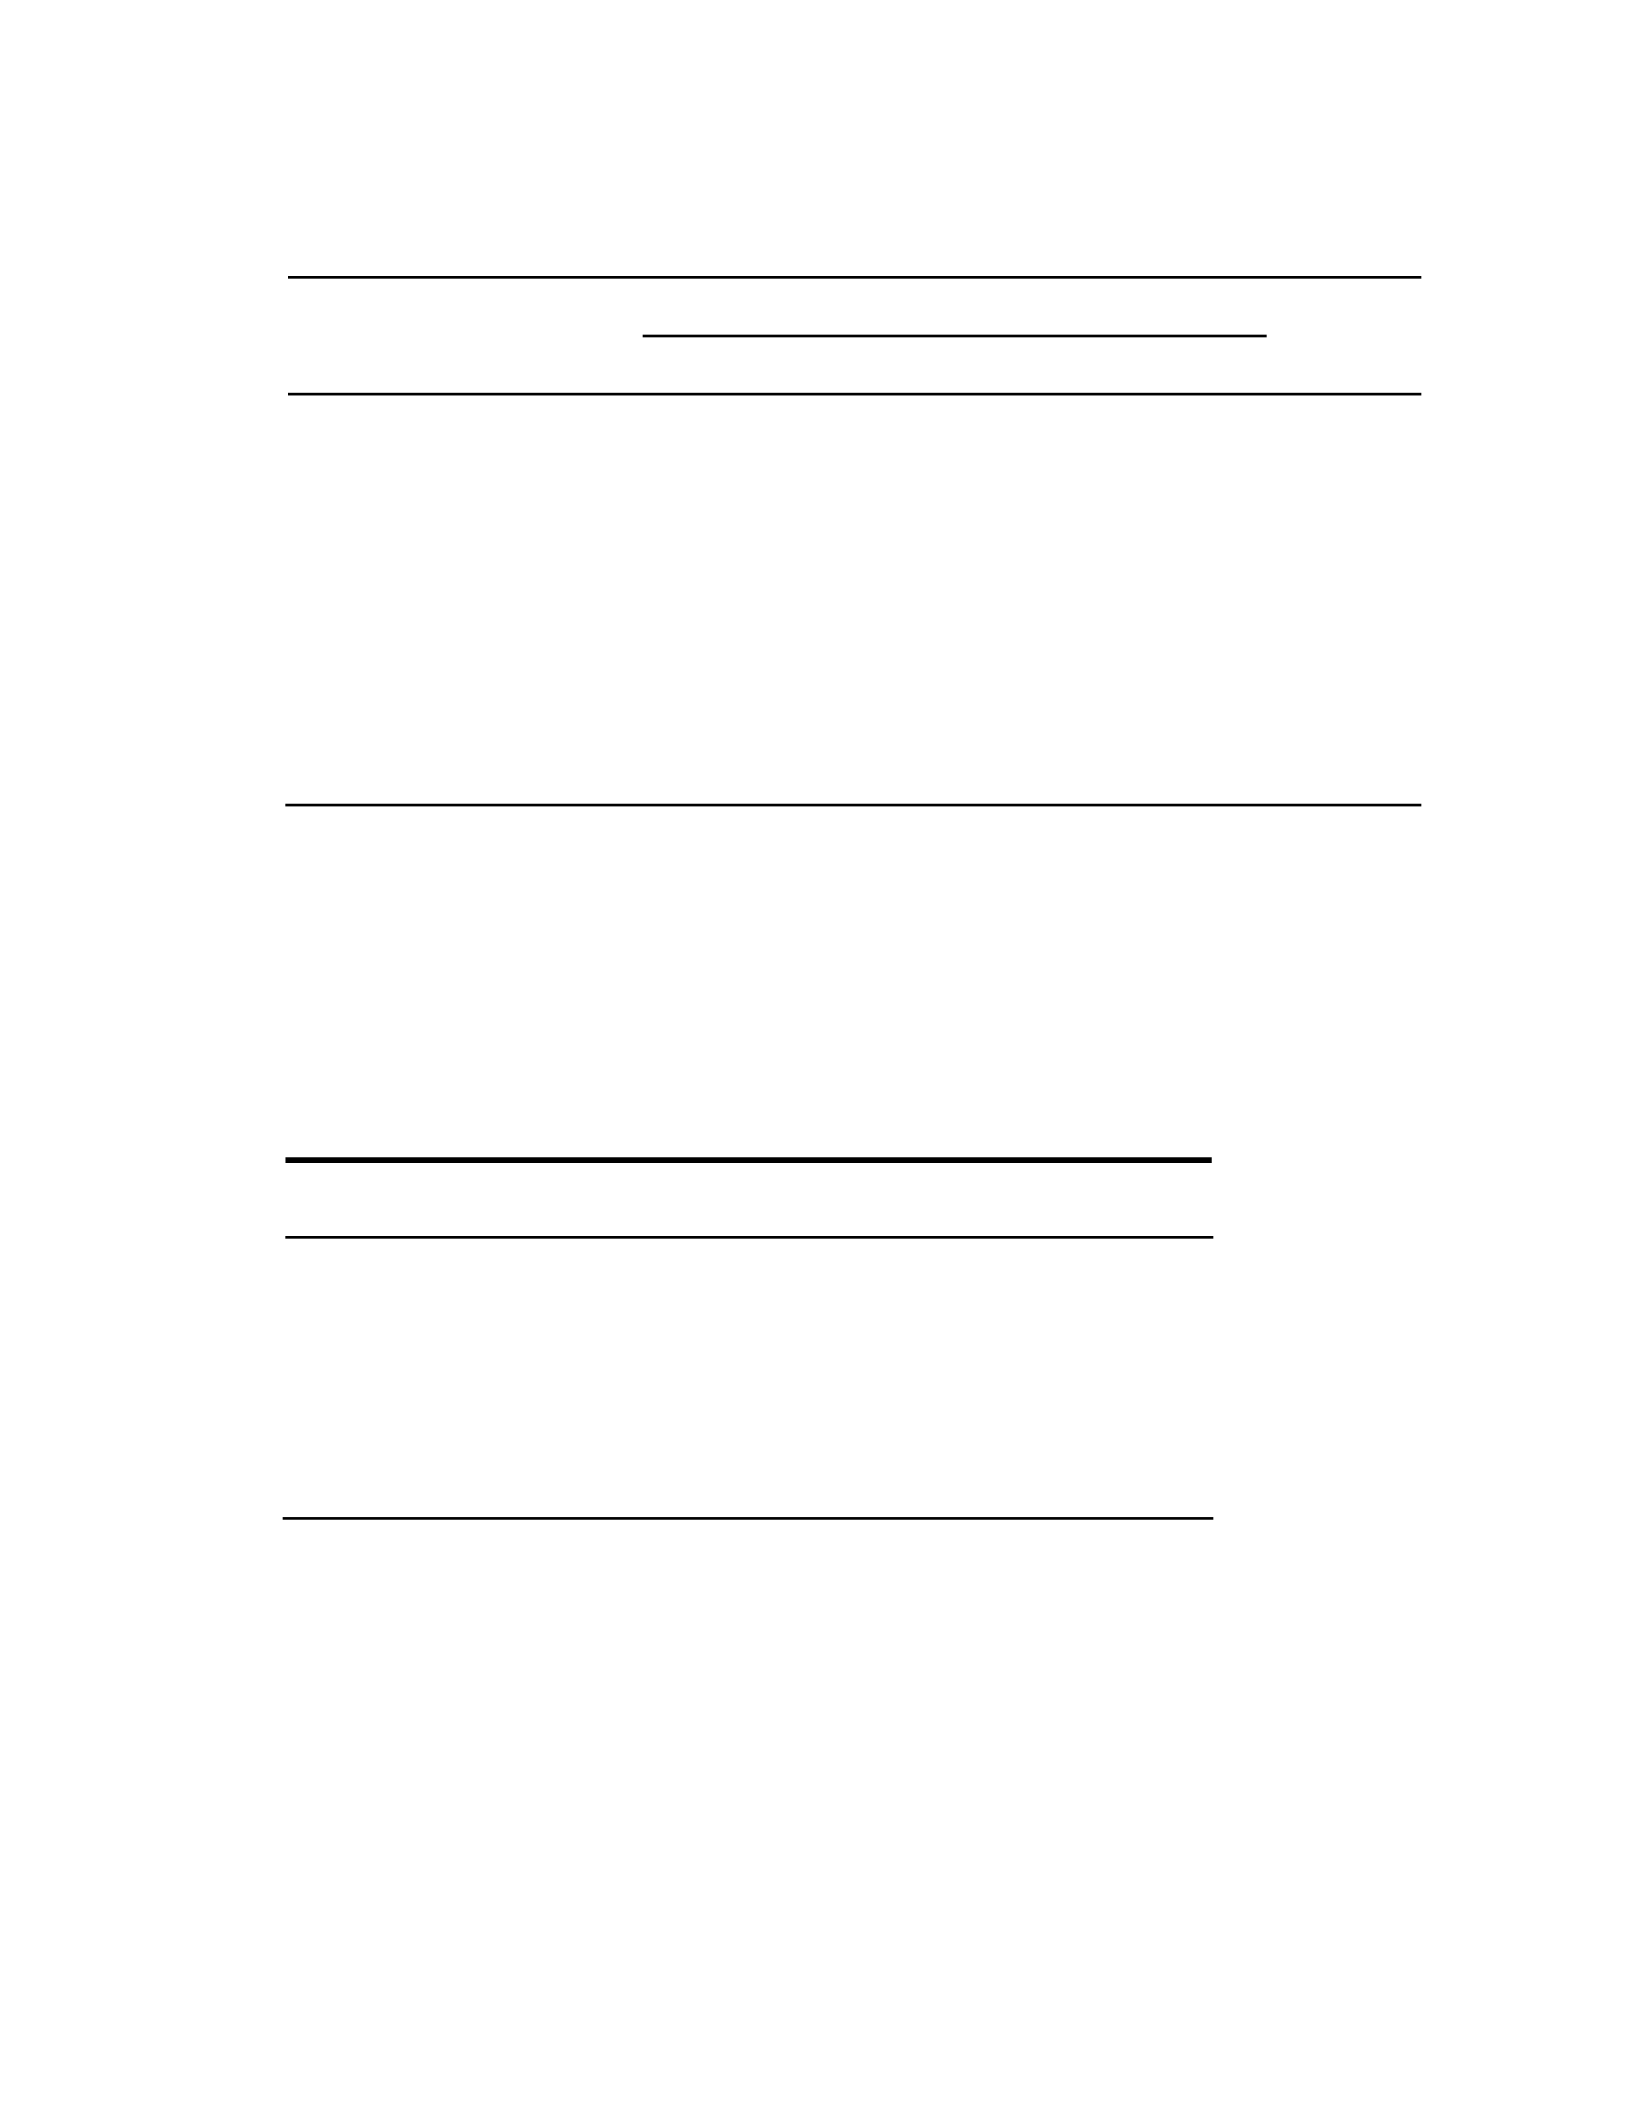
Table Educational attainment versus Vegetables rich in Iron
Highest Education Level
Which vegetables is a rich in iron
Total
Spinach Sukuma wiki Chinsaga
Primary school 7 4 10 21
Percentage 2.0% 1.1% 2.8% 6.0%
Secondary 62 29 32 123
Percentage 17.7% 8.3% 9.1% 35.0%
College and above 123 31 53 207
Percentage 35.0% 8.8% 15.1% 59.0%
Total 192 64 95 351
Percentage 54.7% 18.2% 27.1% 100.0%
Table 4.29 shows that the higher the education attainment the more likely a person
was knowledgeable about iron rich vegetables. Further a chi-square test was done and
the results are indicated in table
Table chi-Square Tests
Value Df Asymp. Sig. (2-sided)
Pearson Chi-Square 9.640a4 .047
Likelihood Ratio 9.222 4 .056
Linear-by-Linear Association 4.848 1 .028
N of Valid Cases 351
The higher the education level the more one is knowledgeable about iron rich foods since
calculated value p= 0.047 is less than the critical value 0.05. In addition, the researcher
sought to find out if the level of education was significant in determining the number of
meals that were sufficient for PLWHA. A chi-square test of independence was used to
140

compare the frequency of number of meals consumed per day and the highest level of
education. Table shows the results.
Table
Chi-Square Tests
Value Df Asymp. Sig. (2-sided)
Pearson Chi-Square 7.000a4 .136
Likelihood Ratio 6.748 4 .150
Linear-by-Linear Association .201 1 .654
No. of Valid Cases 338
Table show the results derived from comparing the level of education and knowing the
number of meals to be eaten by PLWHA. The results show that the level of education
attained is insignificantly related to number of meals consumed in a day. (χ2 (2) = 6.748,
p >0.05). Hence the conclusion that the level of education attained has no significance in
determining the number of meals one is supposed to take there is need for nutritional
education rather than the educational level.
Kenya’s response to the HIV/AIDS pandemic is anchored upon prevention measures which
utilise knowledge on the disease’ modes of transmission and protection strategies aimed at
enabling people to recognize and steer clear of behaviours that increasingly expose them to
contracting the disease (NACC, 2014). Therefore, having adequate and accurate knowledge
especially on transmission pathways as well as prevention approaches is important to avoid
infection and end stigma and discrimination. Although, more than 90% of Kenyans have
heard about HIV/AIDS (NACC, 2014), these findings indicate that comprehensive
knowledge levels among the general population on specific HIV issues is low compared to
other countries in the SSA region where on average, about 25% have accurate knowledge
about how to avoid HIV transmission and prevent the disease’ development. In this context,

comprehensive knowledge refers to correctly identifying sources of iron that can be
locally available and can be used instead of using iron supplementation.
Rapid urbanization and un-employment in Kenya have continued to present challenges
resulting in deteriorating living conditions and rising urban poverty (Okosun et al., 2010).
The most affected population group is the young adults who in the process of searching
for job opportunities to enter cities via urban slums. This creates huge challenges since
slums are served with insufficient health and other socio-economic facilities (Sarode,
2010). Due to inadequate opportunities to gain a decent living coupled with
disillusionments over unemployment; many of them resort to unsafe sexual behaviours.
They often find comfort in trading sex as well as abusing drugs which worsen further
their HIV vulnerability. Other factors that are likely to increase their chances of being
infected with HIV include engaging in inter-generational relationships, lack of
consistency in the use of condoms, forced sex, and trading sex (Allen et al., 2013).
Despite specific programmes targeting the needs of women and children, yet, the
reproductive health needs of young women remain poorly understood (Sanni, 2010). For
instance, this point was well illustrated by the findings of a study conducted in Ethiopia. The
study found young women living in slums to be associated with reproductive health
vulnerability that includes physiological weakness in contracting HIV through heterosexual
contact (UNAIDS, 2009; Macro International, 2008). Another study conducted in Lesotho
demonstrated women’s limited agency in sexual matters. The study found sexual and
physical violence to be the key determinants to the country's severe HIV
epidemic and that both men and women believed that women were not entitled
decline their partners’ sexual advances (Ochako, Ulwodi, Njagi, Kimetu, &
Onyango, 2011). Accumulating research evidence continues to show that young
adults in the SSA region are susceptible to HIV as a result of physiological, cultural,
and behavioural characteristics. For this reason, many studies conducted in Kenya
and Tanzania have predictably accumulated evidence indicating more women than
men are contracting HIV. For example, evidence from studies estimates that more
young women (about three to six times) than young men of the same age contract
HIV (NACC, 2014; NASCOP, 2011; Tanzania Commission for AIDS, 2008).
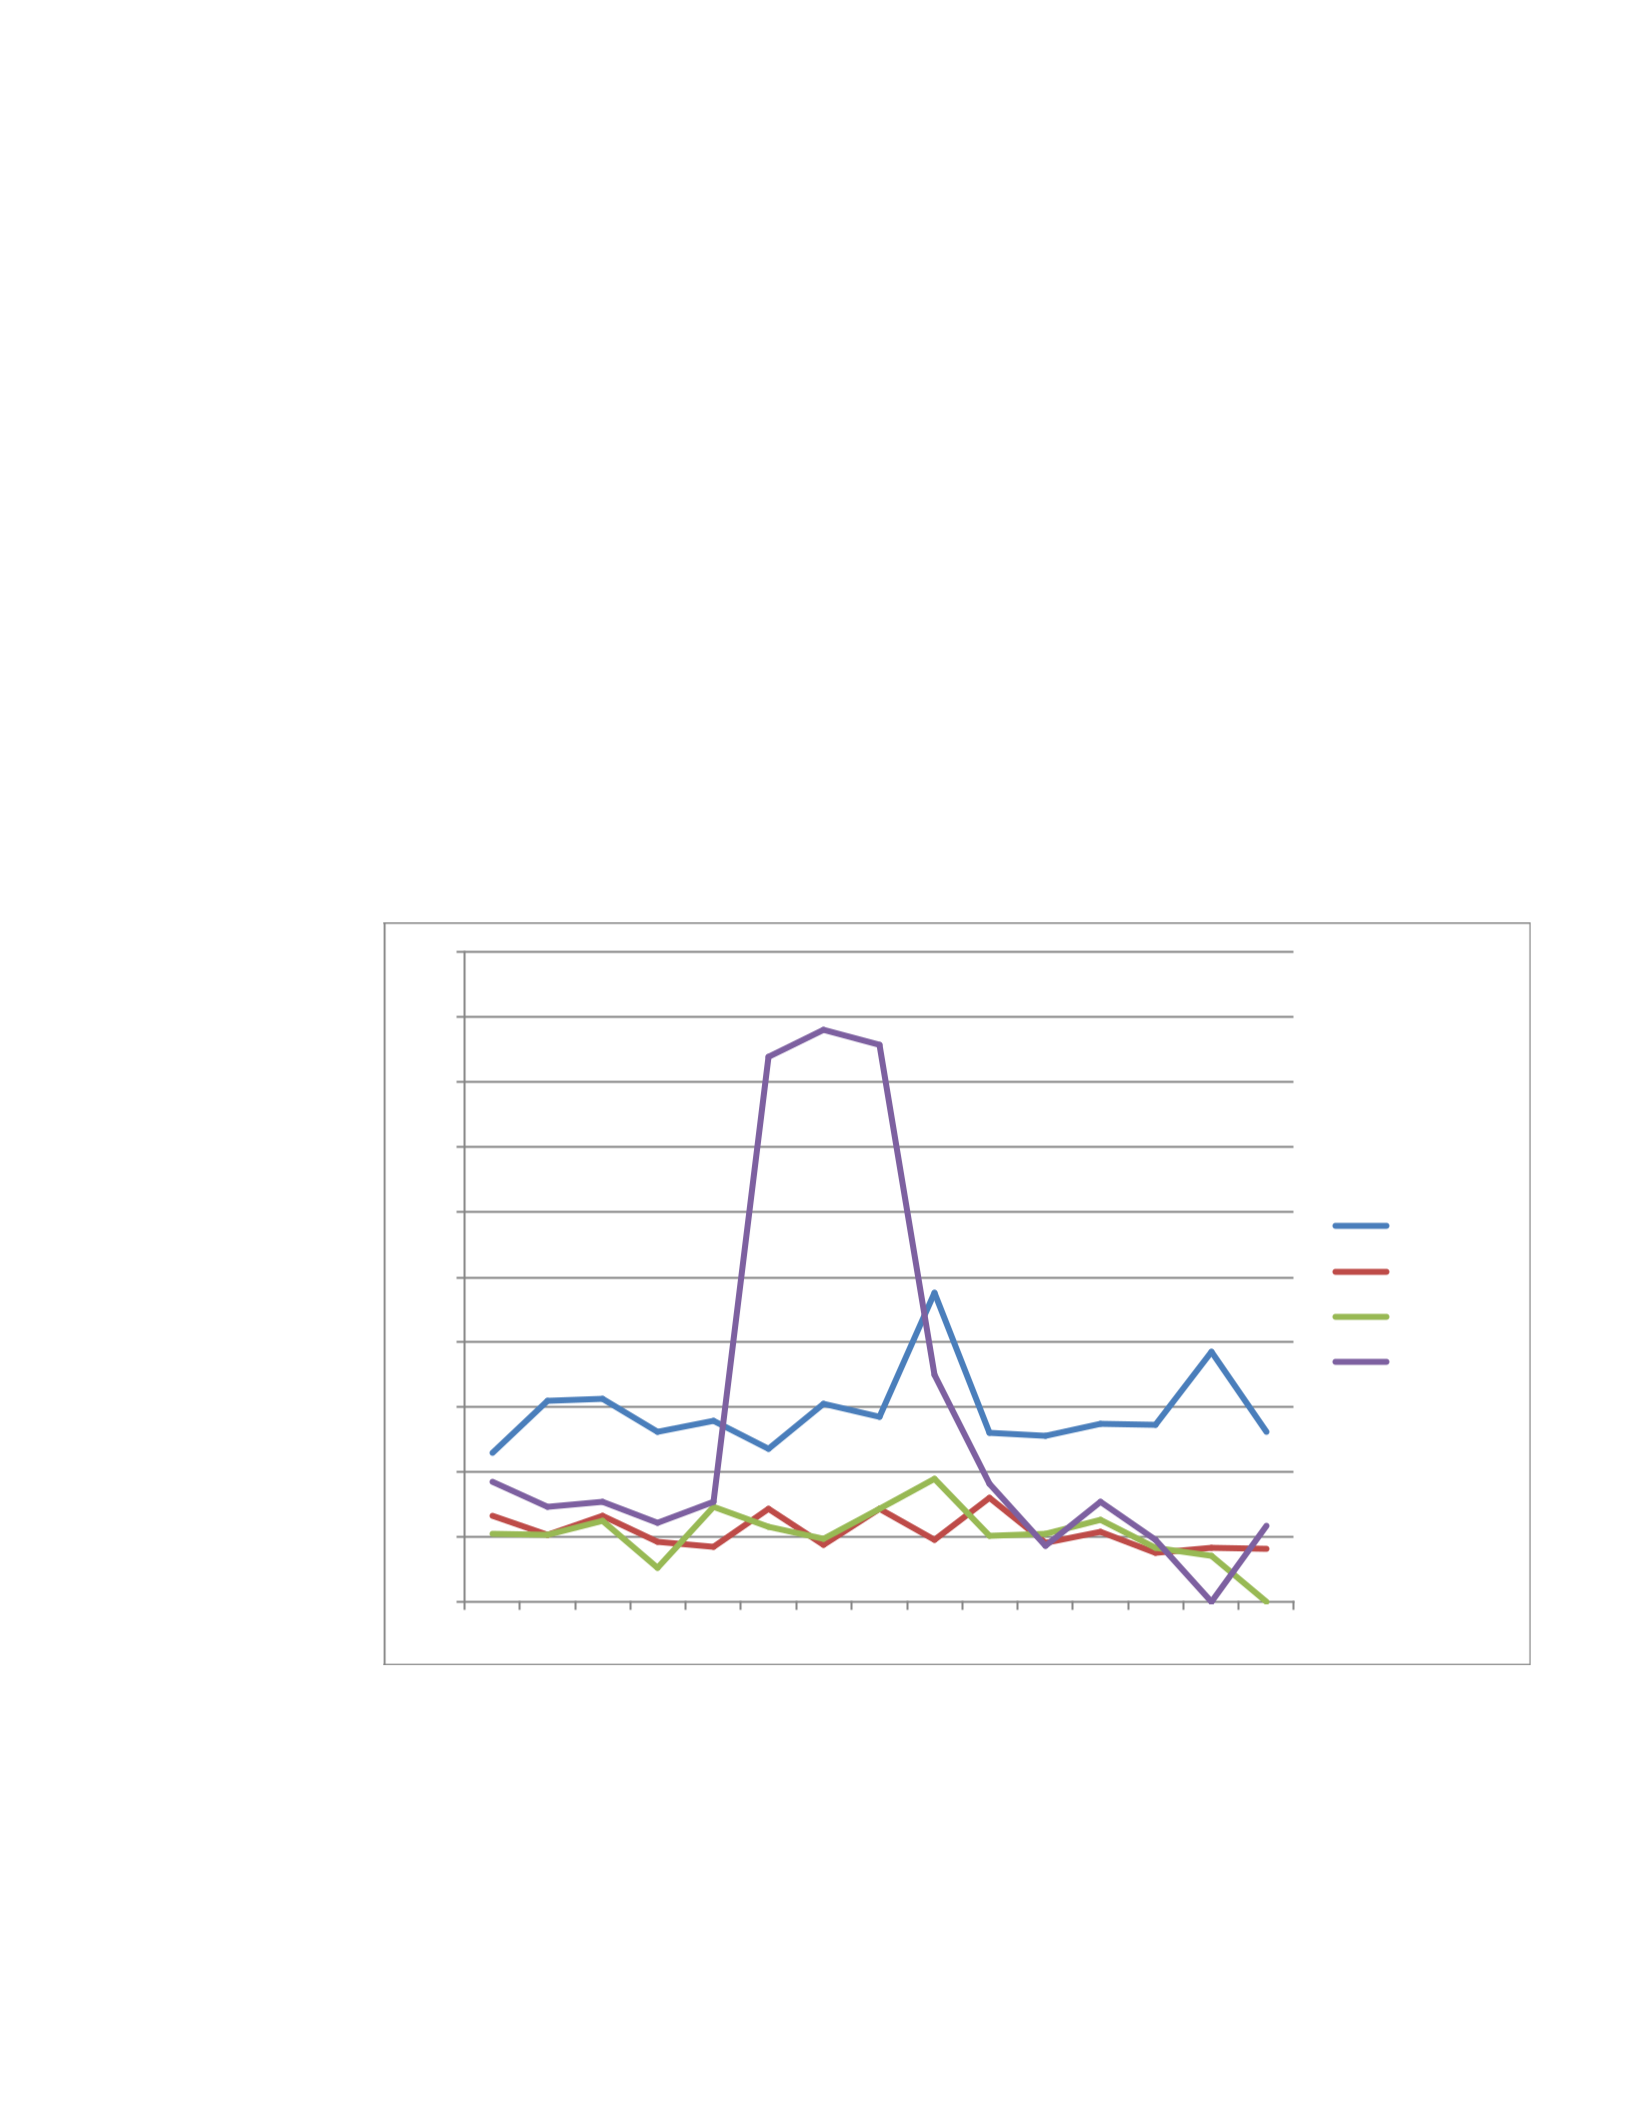
Figure 4.3 shows across tabulation of the knowledge level against participant's
demographic characteristics.
100
90
80
70
60 V/tables
50 Cereals
40
Meals/day
S/Diet
30
20
10
0
1 2 3 4 5 6 7 8 9 10 11 12 13 14 15
Figure 4. 3 Knowledge versus Demographic Participants’ Characteristics

The figure above shows that when viewed against marital status, the majority of the
people had accurate knowledge that PLWHA require a special diet. However, about one-
third of the participants could not be able to answer correctly on vegetables that are rich
in iron. Also, about 10% of the participants answered correctly research testing
participants' knowledge on the cereal which is rich in iron and the appropriate number of
meals per day. The factors associated with a high level of knowledge include marital
status and level of education which produce spikes on the graph.
As expected, the findings show that young people have comprehensive knowledge of
local foods that are rich in iron compared to the old people who lack correct nutritional
knowledge on how to combat HIV. Unlike prior studies, this study found that females
edge males marginally on the knowledge of local foods. However, men are more
knowledgeable on vegetables and cereals that are rich in iron while women are more
knowledgeable on the appropriate number of meals per day for PLWHA and that people
infected with HIV need a special diet.

