


1
Chapter 1: Introduction to the Study
Everyone will experience the loss of a loved one sometime within his or her
lifetime. A person can experience loss due to a divorce, separation, breakup, or
estrangement (Breen & O’Conner, 2011). An individual may experience loss of capacity,
loss of a job, or loss caused by natural or human-caused disasters (Humphrey, 2009). An
individual’s response to such a loss is unique (Thirsk & Moules, 2012), and not all
individuals will seek mental health services to assist them with their grief. However,
some people do seek out such services. According to the National Institute of Mental
Health (2007), only 18% of the United States population used mental health services.
The demand for grief counseling in the United States will be on the rise due to a
variety of reasons in the near future. For instance, the aging baby boomer generation
worldwide is estimated to be at 72 million people aged 65 years old or older in the year of
2030, and is expected to grow to be 19% of the population (Hooyman & Kiyak, 2005;
U.S. Department of Health and Human Services, n.d.). Due to the aging generation, we
will see an increase in deaths in the baby boomer population (Hooyman & Kiyak, 2005).
In addition, we might see an increase in the baby boomer population seeking out grief
counselors due to a disability, loss of a loved one, or grieving the loss of quality of life
(Hooyman & Kiyak, 2005; Ober, Granello, & Wheaton, 2012). Ober, Granello, and
Wheaton indicated the request for grief counselors will be on the rise due to the aging
Baby Boomers successive losses and the grief they experience. Breen (2010) indicated

2
counselors are required to be educated and trained to provide effective and appropriate
grief counseling to clients.
According to Kaskie, Imhof, and Wyatt (2008), one of every five older persons in
America each year experiences a mental health disorder. Robb, Haley, Becker, Polivka,
and Chwa (2003) suggested there is an increase in the use of mental health services in the
older adults’ population ranging in the ages of 65 years and older. The Seniors Mental
Health Access Improvement Act of 2013 (S. 562; bipartisan counselor coverage bill), has
been assigned to a congressional committee (Barstow & Terrazas, 2012). The bill
proposes to cover state-licensed counselors under the same terms as clinical social
workers. The passing of this bill is important because the baby boomer generation is
reaching Medicare eligibility. Therefore, it is important for Medicare to recognize
counselors as providers of mental health services so they can assist the aging population
with their grief and loss issues (American Counseling Association, 2006).
Furthermore, veterans are returning home from war in Iraq and the Middle East
with presenting issues of grief and loss due to the loss of members of their units and
friends (Papa, Neria, & Litz, 2008), as well as with sometimes traumatic injuries or
disabilities. As a result, Veterans reported they are grieving the loss of how life used to
be before their injuries (e.g., Papa et al., 2008). Marshal (2006) stated many veterans are
returning home from war with mental health issues pertaining to grief and loss. With the
changes in the legislature, counselors can apply for positions in the Department of

3
Veterans’ Affairs clinics to assist Veterans in need with their presenting issues (American
Counseling Association, 2007).
Ober et al. (2012) noted a gap in the research literature that examines master’s-
level counseling students’ self-reported competency, training, and education in providing
grief counseling. Many people deal with grief issues that prevent them from having joy or
purpose in their lives and that leaves them unable to engage in positive opportunities or
relationships (Neimeyer & Currier, 2009). This study is significant and timely in that it
examines CACREP-accredited master’s counseling students’ self-reported competency,
training, and education in providing grief counseling. The implications for positive social
change arising from my research may be to incorporate and promote education and
training in grief theories and skills in a majority of counseling programs, and to provide
motivation to incorporate professional standards for grief training and practice in the
mental health counseling field.
In this chapter, I present the background for my study, the problem that I
addressed, relevant literature on my topic, and my research questions and hypotheses.
Additionally, I discuss my theoretical framework which draws from Bowlby’s (1980)
work on attachment theory in relation to the social problem, the nature and design of my
study, and definitions of the terms used. I then considered my assumptions and the
delimitations, limitations, and the significance of my research. I conclude the chapter
with a summary.

4
Background of the Study
People commonly experience grief as a result of a difficult life transition or loss.
A person can experience grief due to a divorce, separation, breakup, or estrangement
(Breen & O’Conner, 2011). An individual may also experience grief due to loss of
capacity, loss of a job, or loss caused by natural or human-caused disasters (Humphrey,
2009). Loss and transition are two of life’s constants (Martin & Doka, 2000). No one can
expect to live a life free of challenges, disappointments, change, or loss (Humphrey,
2009). Grief is one’s own personal experience of loss and is manifested in different ways
due to the individual’s own life experiences (Archer, 2001).
Grief is an emotion that is usually generated by a critical life event experience due
to a loss. Grief can apply to non-death related and death-related losses (Doughty Horn,
Crews, & Harrawood, 2012). The experience of grief is unique and multidimensional
(Granek, 2010). Researchers have identified and reported common grief responses as
cognitive, affective, physical, behavioral, and contextual influences that can affect
individuals in a negative way (e.g., yearning for the deceased) or in a positive way (e.g.,
feeling a sense of relief; Cordaro, 2012; Harrawood, 2012).
Individuals who have experienced some type of loss may have grief symptoms
such as sorrow, numbness, depressed mood, lethargic behavior, sleep disturbances, loss
of appetite, preoccupation, disbelief, anger, guilt, decreased interest in socializing, and
the loss of interest in life experiences that use to be pleasurable to the individual

5
(Cicchetti, 2010; Freeman & Ward, 1998). Neimeyer and Currier (2009) noted that an
individual’s untreated grief issues may result in suicidal ideation, functional impairment,
cardiac events, substance abuse, or issues with high blood pressure. However, if an
individual gradually adapts and integrates the loss into their life, he or she may
experience less intense and less frequent grief symptoms (Humphrey, 2009).
According to Ober et al. (2012), the demand for grief counseling services in the
United States will be on the rise. Ober et al. surveyed 369 licensed professional
counselors (LPCs) in a Midwestern U.S. state on the grief training they had completed,
their personal and professional experiences with grief, and their self-assessment of their
grief counseling competencies. They found that most of the participants had not had any
course on grief counseling (Ober et al., 2012). The authors urged that additional research
be conducted on the education and training on grief counseling provided by counselor
education programs. Research by Breen (2010) also indicated that counselors need to be
educated and trained to provide effective and appropriate grief counseling to the clients
they serve.
However, there are several challenges in assuring that mental health counselors
are prepared to meet the increased demand for providing grief counseling services. For
instance, there is a lack of professional standards for grief training and practice in the
mental health counseling field (Breen, 2010). Additionally, there is limited grief
education and training within counseling programs (Doughty Horn et al., 2012; Ober et

6
al., 2012). Furthermore, there is a need for defining competency standards in grief
counseling within the counseling profession (Kaplan et al., 2009). Current research has
indicated that many counselors report uncertainty in their ability to provide effective grief
counseling to clients, and has indicated the need to establish grief counseling
competencies (defined below) through education and training in counselor education
programs (Doughty Horn et al., 2012; Ober et al., 2012).
Establishing counselor competencies is an important component in the counseling
profession to effectively and appropriately help clients (Doughty Horn et al., 2012;
Morgan & Roberts, 2010). Moreover, counselor competency assists in promoting self-
regulation and training within the counseling profession (ACA, 2014). According to
McGlothlin and Davis (2004), the Council for Accreditation of Counseling and Related
Educational Programs (CACREP) is the largest counseling accreditation body.
McGlothlin and Davis (2004) stated accreditation standards ensure quality education in
the counseling profession. However, grief and loss competencies and training are not
mentioned in the current CACREP standards (CACREP, 2016; Doughty Horn et al.,
2012).
Crisis and trauma counseling competencies, multicultural counseling competency,
career counseling competencies, and advocacy competencies (social justice) were not
addressed in CACREP core courses until counseling demands and client needs became
evident in the counseling profession (Doughty Horn et al., 2012; Sue & Sue, 2008). Ober

7
et al. (2012) stated different types of competency standards have been accepted by the
counseling profession and have been integrated into CACREP-accredited counseling
programs of study in response to clients’ needs. Some experts have called for research on
course offerings, coursework, and students’ grief counseling competency to determine
whether competency standards should be accepted by the counseling profession
(Cicchetti, 2010; Ober et al., 2012). In addition, course offerings, coursework, and
students’ grief counseling competency should be investigated to determine if they should
be integrated into CACREP-accredited counseling programs of study to ensure effective
care to meet clients’ needs (Cicchetti, 2010; Ober et al., 2012).
According to the American Counseling Association’s (ACA) “Code of Ethics”
(2014), counseling competency is important for counselors to establish within the
profession. The ACA “Code of Ethics” stated that counselors need to be properly trained
to be competent to assist those in need ethical and effectively in Section Standard C.2.,
including working with clients that have presenting issues of grief and loss in Section
Standard A.9. (Doughty Horn et al., 2012). Sadeghi, Fischer, and House (2003) suggested
that if counselors do not have adequate training they might lack the skills to address the
presenting issues of a client.
The development of grief counseling competencies is an important issue in the
mental health counseling profession due to the projected future need for grief counselors
or counselors who are competent in working with clients who are experiencing grief

8
(Haley, Kasl-Godley, Larson, Neimeyer, & Kwilosz, 2007). Currently, the counseling
profession lacks an established framework of grief counseling competencies that is
similar to the established framework our profession has on multicultural counseling
competencies (ACA, 2014). Gamino and Ritter (2012) noted counselors approach grief
with their own experiences or biases. Therefore, grief counseling competencies should be
a requirement in the counseling profession to effectively manage one’s own responses to
grief counseling and to provide effective treatment for clients. I sought to provide
additional research on master’s students’ self-assessment of competency in grief
education and training in CACREP-accredited counseling programs.
Problem Statement
Ober et al. (2012) noted there is currently a gap in the research literature that
examines master’s counseling students’ self-reported competency, training, and education
in providing grief counseling. According to Werth and Crow (2009), grief is an
experience that essentially all people experience during their lifetimes, and due to the
aging baby boomers and successive losses, the need for grief counselors or counselors
who are competent in working with clients that are experiencing grief is in high demand
and growing (Marshall, 2006; Papa et al., 2008).
Collier (2011) stated that 10-15% of individuals struggle to adjust to the loss of a
loved one. According to Neimeyer and Currier (2009), many people deal with debilitating
grief that prevents them from having joy or purpose in their lives and that leaves them

9
unable to engage in positive opportunities or relationships. Howarth (2011) stated that the
lack of effective grief counseling may have negative consequences for a client such as
their grief reactions may become more painful and debilitating. Therefore, I believe that
my study of CACREP master’s counseling students’ self-reported competency, training,
and education in providing grief counseling is significant and timely.
Purpose of the Study
The purpose of this quantitative study was to examine whether master’s
counseling students in CACREP-accredited programs perceive that they have been
adequately trained in identifying clients’ presenting grief issues and in providing grief
counseling to clients in need. These participants were chosen to examine how master’s-
level counseling students rate themselves concerning the education or training they
received about grief theories or counseling skills related to issues of grief interventions in
their CACREP-accredited formal coursework.
I used Cicchetti’s (2010) Grief Competency Counseling Scale (GCCS), which is
an adapted version of the Death Counseling Survey (DCS; Charkow, 2002). Charkow
initially designed the DCS to measure counselors’ perceptions of their training and ability
to assist clients who were experiencing grief due to death. Cicchetti revised the DCS and
labeled the survey the GCCS to reduce possible participant’s bias due to the DCS title. In
my study the independent variables were demographic variables (gender, age, race, and
ethnicity), coursework, and practicum or internship setting. The four grief competency

10
sub scales on the GCCS were the dependent variables, and the covariate was course
offering.
Nature of the Study
The research method used for my dissertation study was quantitative. The
research design I used is a non-experimental, one shot survey comparative design
(Cicchetti, 2010). I ran the power for the MANOVA using G*Power 3.1.7 software. I
used a medium effect size F test of .25, alpha level of .05, power of .80, and 6 degrees of
freedom. The analysis indicated that a sample size of at least 225 participants was
required (Faul, Erdfelder, Lang, & Buchner, 2007), so, calculating for a low response rate
of 20% (225/.2 = 1125), this required that the survey needed to be sent to at least 1,125
potential participants (S. Jackson, personal communication, August 13, 2015). Basing
this study on a very low response rate takes into account these variables and other
variables that may not have been considered (S. Jackson, personal communication,
August 13, 2015).
Criterion sampling (Franfort-Nachmias & Nachmias, 2008) was used for this
study and included the population of master’s-level students in CACREP-accredited
counseling programs. The data collection method that I used in my dissertation study is
the survey method. The GCCS and the DDS were used to collect data (Cicchetti, 2010).
The GCCS provided participants with the ability to self report on four sub-scales
(personal competencies, conceptual skills and knowledge, assessment skills, and

11
treatment skills) of perceived competency pertaining to their education or training in grief
counseling. Combining each of the subscales scores provided a total score. Mean scores
were calculated by dividing the subscale scores by the number of items. The DDS
provided data about each participant’s gender, age, race, ethnicity, coursework, and
practicum or internship setting. Students enrolled in Practicum or Internship courses
were asked to participate in the study. A convenience procedure was used to obtain
participants by writing to program directors of CACREP-accredited counseling programs
who were asked to forward the survey to their students. Students were invited to
participate by completing an online survey via SurveyMonkey. The independent
variables were the demographic variables (gender, age, race, and ethnicity), coursework,
and practicum or internship setting. The four grief competency sub scales on the GCCS
were the dependent variables, and the covariate was course offering, whether the
participant’s course curriculum offered coursework in grief counseling theories and
practice.
The research method and data collection method were both appropriate for my
study, because the methods allow the specific research questions to be answered through
the participants’ responses to the questions on the survey instruments in regards to the
participants perceived competency through their education or training in grief counseling
in which the participants obtained in their formal coursework in their CACREP
counseling program. A true experimental design or a qualitative design is not appropriate

12
for this study. The survey design is appropriate, because it allows me to test the
hypotheses.
Research Questions and Hypotheses
My overall general research question was adapted from Cicchetti’s (2010) study:
How competent do master’s-level counselors view themselves regarding the education or
training they received in grief theories or counseling skills in their CACREP-accredited
studies? My sub-questions and related hypotheses included:
RQ1. How do the demographic variables (e.g., gender, age bracket, race, and
ethnicity) relate to perceived grief counseling competency?
H
o
1: There is no significant (α = .05) interaction effect among the demographic
variables and perceived grief counseling competency.
H
1
1: There is a significant interaction effect among the demographic variables
and perceived grief counseling competency.
This question was investigated using a 4-way MANOVA with demographic
variables (gender, age bracket, race, and ethnicity) as independent variables and the four
grief competency sub scales on the GCCS as dependent variables.
RQ2. Controlling for course offerings (i.e., whether the participant’s course
curriculum offered coursework in grief counseling theories and practice), what is the
relationship between coursework and grief counseling competency?

13
H
o
2: There is no significant (α = .05) positive relationship between coursework
taken and the four grief counseling competency scales, controlling for course offerings.
H
1
2: There is a significant positive relationship between coursework taken and the
four grief counseling competency scales, controlling for course offerings.
This question was investigated using a MANCOVA where the independent
variable was coursework; the dependent variables were the four grief competency sub
scales on the GCCS, and the covariate was course offering.
RQ3. What is the relationship between practicum or internship setting and
perceived grief counseling competency?
H
o
3: There is no significant (α = .05) relationship for clinical setting and
perceived grief counseling competency.
H
1
3: There is a significant relationship for clinical setting and perceived grief
counseling competency.
This question was investigated using a MANOVA whereas the independent
variable was practicum or internship setting and the four grief competency sub scales on
the GCCS were the dependent variables.
Theoretical Framework
The theory that informed this quantitative study is modern grief theory. Modern
grief theory is based on John Bowlby’s work on Attachment Theory (Carr & Cortina,
2011). Bowlby (1980) stated Attachment Theory can be used as a conceptual framework

14
for understanding grief (Cicchetti, 2010). According to Bowlby, a person that is
responsive to another person’s needs enables the individual to develop a sense of security
and trust. Bowlby described attachment as a psychological connectedness between a
significant other. Therefore, when the attachment to another person ends due to
separation or death; the remaining significant other than grieves (Bowlby 1980). In the
relational approach to master students’ self-assessment of competency in grief education
and training, Breen (2010) addressed the level of efficacy that develops when grief is
presented in curricula, counselors understand modern grief theories, and implement grief
interventions in their counseling practices. This will be discussed in greater detail in
Chapter 2.
Definition of Terms and Variables
Advocacy: Becoming actively involved in a cause to promote positive social
change and thus to put counseling in action (Osborne, Collison, House, Gray, Firth, &
Mary Lou, 1998). Counselors take the role of promoting societal change by acting as an
agent and working towards an intervention on behalf of the profession, an organization,
and their clients (West, Bubenzer, Osborn, Paez, & Desmond, 2006). Advocating is a
single person or a group of people working together challenging beliefs in our society,
questioning the status quo, challenging the rules and regulations that are in place, and
protesting to influence change through awareness and education (Osborne et al., 1998).

15
Council for Accreditation of Counseling and Related Educational Programs
(CACREP): A specialized accrediting body for professional preparation in specific
graduate degree programs within the accredited institution (CACREP, 2016; McGlothlin
& Davis, 2004). There are well-defined criteria outlining the national standards and
training of skills to which graduate students must be held accountable (CACREP, 2016).
The vision of CACREP is to promote excellence and to provide leadership through its
accreditation standards by continually improving programs and preparing professionals to
provide services to promote optimal human development (Adams, 2006). CACREP
program assessments are conducted to ensure that all components of the program meet
the CACREP standards in order for the program to receive accreditation by CACREP
(CACREP, 2016). The CACREP accreditation provides recognition that the quality and
content of the program meets the standards set by the profession to reflect the needs of a
dynamic, complex, and diverse society (CACREP, 2016). Students enrolled in a
CACREP-accredited program can be assured the appropriate knowledge and skill areas
are included in the program and the program is professionally and financially stable
(Adams, 2006). Furthermore, graduating from a CACREP-accredited program constitutes
an important credential and distinguishes counselors as having completed a program that
meets the standards of excellence for the profession (CACREP, 2016).
Counselor competency: According to the American Mental Health Counselors
Association (AMHCA, 2010) and the ACA (2014) “Code of Ethics”, is important for

16
counselors to gain competence in the areas of counseling that they provide to the ones
they serve (Morgan & Roberts, 2010). According to the AMHCA (2010) Principle 7,
counselors are expected to recognize their boundaries on their competencies and the
limitations on their expertise. Furthermore, counselors are to provide services and use
techniques that they are qualified by education, training, techniques, or experience to
provide (AMHCA, 2010). The ACA (2014) “Code of Ethics”, Section C.2.a. Boundaries
of Competence stated counselors should practice only within their boundaries of
competence based on their education, training, state and national credentials, and
professional experience.
Grief: According to Humphrey (2009), grief is an emotion that is generated by an
experience of death or non-death-related loss. Grief is often characterized by sorrow or
distress (Jakoby, 2012). Grief is unique to the individual and multidimensional in
responses and contextual influences (Humphrey, 2009). Grief is the process of
experiencing the reaction to the perception of the loss (Cicchetti, 2010; Doughty Horn,
Crews, & Harrawood, 2013; Rando, 1995).
Grief counseling: Grief counseling refers to the therapeutic work with clients who
present with grief symptoms due to death or non-death-related loss (Humphrey, 2009).
Grief counseling may be used in individual, group, couples, or family counseling
sessions. There are theoretical approaches and interventions that counselors may use to
assist grievers to manage their responses (mentally, emotionally, physically, or

17
spiritually) to the loss they have experienced (Cicchetti, 2010; Doughty Horn, Crews, &
Harrawood, 2013; Rando, 1995).
Grief counselor competencies: Grief counseling competency is when a counselor
obtains and demonstrates that one has the education, training, techniques, experience,
knowledge, and skills to assist the needs of their grieving client. In this study, the grief
counseling competencies are based on the GCCS assessment instrument developed by
Cicchetti (2010), which is an adapted version of Charkow’s (2002) DCS. The GCCS
included five scales: Personal Competencies, Conceptual Skills and Knowledge,
Assessment Skills, Treatment Skills, and Professional Skills (Cicchetti, 2010). The
instrument in this study is a self-report survey and participants were asked to report the
level of agreement with survey items. The survey was used to collect demographic
information.
Holistic: In this study, holistic refers to the whole person in regards to his or her
mind, body, emotions, and spirit that are all interdependent parts. When all the
interdependent parts are in balance, one achieves optimal health and well-being
(Chidarikire, 2012). However, if one part is not in balance, the other parts will be affected
(emotionally, physically, or spiritually) in which can negatively affect one’s overall
health and well-being (Chidarikire, 2012).
Master’s-level student requirements in a CACREP-accredited mental health
counseling programs: Beginning July 1, 2013, all CACREP-accredited “mental health

18
counseling programs must require a minimum of 60 semester credit hours or 90 quarter
credit hours for all students to meet the academic unit” requirement set by the CACREP
standards (CACREP, 2016, p.5). In addition, the graduate-level core coursework must be
in the following 8 content areas: (a) professional counseling orientation and ethical
practice, (b) social and cultural diversity, (c) human growth and development, (d) career
development, (e) counseling and helping relationships, (f) group counseling and group
work, (g) assessment and testing, and (h) research and program evaluation (CACREP,
2016).
Master’s-level student practicum requirements in a CACREP-accredited mental
health counseling program: Students must complete a supervised practicum experience
with a minimum total of 100 clock hours of which 40 of those hours must be direct client
contact hours providing face-to-face counseling (CACREP, 2016). During practicum, the
student must also obtain one hour per week site supervision and 1 ½ hours per week of
program faculty group supervision (CACREP, 2016).
Master’s-level student internship requirements in a CACREP-accredited mental
health counseling programs: The program also requires completion of a supervised
internship experience with a minimum total of 600 clock hours of which 240 of those
hours must be direct client service hours providing face-to-face counseling and leading
groups (CACREP, 2016). During internship, the student must also obtain one hour per

19
week site supervision and 1 ½ hours per week of program faculty group supervision
(CACREP, 2016).
Unresolved grief: Unresolved grief is when the grief lasts longer than usual for
the individual’s cultural background (Field, 2006). Often times, unresolved grief is
described as grief that will not go away or that it is interfering with the individual’s
capabilities to care for one’s self daily (Field, 2006). Unresolved grief is abnormal,
pathological, or traumatic grief with loss of feelings, denial, and repression (Cicchetti,
2010; Jacobs, 1999).
The independent variables for my study included demographic variables (gender,
age, race, and ethnicity), coursework, and practicum or internship setting.
The dependent variables for the study include the following:
Level of Competencies, Skills, and Knowledge on the GCCS: Measures the
Personal Competencies, Conceptual Skills and Knowledge, Assessment Skills, and
Treatment Skills estimated by self-using the GCCS on a 5-point Likert scale that was
converted to a mean score to obtain the four subscales on the same 5-point Likert scale,
because each item was measured on a different number of items.
Total Score on the GCCS: An interval measurement on overall competencies,
skills, and knowledge estimated by self on the GCCS, using a 5-point Likert scale on the
37 questions resulting in a range in score 37-185.

20
The covariate for this study was whether the participant’s course curriculum
offered coursework in grief counseling theories and practice. For this study, the covariate
was held constant in examining the relationship between perceived grief counseling
competency and coursework. The aforementioned was measured by the four sub scales
on the GCCS.
Assumptions
The assumptions made with regard to conducting this study are that the
instruments used to gather data in the study accurately measured the variables as intended
(Cicchetti, 2010). Other assumptions were made in regard to the participants who are
assumed to be attending CACREP-accredited counseling programs and completed all of
their CACREP core course requirements for master’s-level counselors in training. It was
assumed that participants understand and answered all the questions with complete
honesty. The data for this study were collected, analyzed, and reported in an ethical
manner (Cicchetti, 2010).
Limitations
The study had a few limitations. A limitation of using quantitative methods for the
research study is that one cannot obtain an in-depth understanding of the participants
lived experience (Creswell, 2009). A limitation of using the non-experimental, one shot
survey research design is that the respondents are limited in their response to those
permitted on the GCCS (Creswell, 2009). Frankfort-Nacmias and Nacmias (2008) stated

21
content validity is determined by the degree to which the questions on an instrument are
representative of what the instrument was designed to sample. The GCCS was designed
to assess master’s-level student’s competency in grief counseling (Cicchetti, 2010). The
questions on the instrument are representative of what the instrument was designed to
sample. The data gathered were provided by the master’s-level counseling students about
their perceptions on their grief counseling competencies pertaining to their education and
training.
The data were gathered via self-report which may not be the most objective form
of evaluation (Janesick, 2011). Participants may have answered with bias in which their
answer may reflect negatively upon their institution, therefore, a noted limitation in the
study (Janesick, 2011). The participants were asked to be honest when giving their
answers on their survey questions.
The participants were recruited from CACREP-accredited master’s-level
counseling programs through faculty members from each institution. Therefore, it is
difficult to be certain that all eligible practicum and internship students were informed of
the study in order to participate. The study is intended for master’s-level counselors in
training from CACREP-accredited institutions and did not intended to gather data from
master’s-level counselors in training from non-CACREP-accredited institutions. Due to
the recruitment criteria, generalizability was limited to CACREP-accredited master’s-

22
level counseling students. Therefore, the findings cannot be generalized to any larger
population.
Time constraints are a noted limitation when using an online survey design to
obtain participants responses (Wilson, Petticrew, Calnan, & Nazareth, 2010). According
to Wilson et al. (2010), response rates for online survey design studies can be low;
therefore, it may take time for me to obtain a large enough sample size of participants.
With that in mind, scheduled follow-up e-mails were used to request participation in
order to obtain the required sample size of participants for this study.
Scope and Delimitations
Criterion population sample was used in this study due to the scope of the
research study. Master’s-level counseling students in CACREP-accredited programs that
are enrolled in their practicum or internship course were invited to participate in this
survey research study. Participants were asked to examine their perceptions on their
education and training in grief counseling in their CACREP counseling program.
CACREP-accredited master’s-level counseling programs were selected for this study, due
to the education and training structured requirements of all its accredited programs. I
delimited non-CACREP counseling programs due to differences in academic education
and training requirements. The populations I am not studying are doctoral level
counseling students or licensed professional counselors. The reason I delimitated the
aforementioned populations is because those groups may have obtained grief education

23
and training from workshops, conferences, or continuing education classes after their
master’s-level training. Therefore, I delimited the findings and they cannot be
generalized to doctoral level counseling students, licensed professional counselors, or
non-CACREP counseling program students.
Significance of the Study
The significance of this proposed dissertation study is unique because it addresses
an important and under-researched area of the competency of Master’s-level counseling
students in providing grief counseling (Doughty Horn et al., 2012; Ober et al., 2012).
Breen (2010) noted there is a shortage of grief counselors or counselors who have been
trained in grief theories and interventions in the counseling profession. There is little
evidence that graduate counseling programs require coursework in grief counseling (Ober
et al., 2012).
In addition, there are minimal research studies conducted pertaining to grief and
loss theories, interventions, education, and training in the field of mental health
counseling or in the other helping professions (Doughty Horn et al., 2012). Counselor
competency is the professional responsibility of all members of the counseling profession
(ACA, 2014; Cicchetti, 2010). The results from the study provide insight into the
students’ perceived competency in grief training and education through self-reports.
According to Ober, Granello, and Wheaton (2012), everybody experiences some
type of grief, loss, or transition within his or her lifetime. Therefore, it is understandable

24
that grief counseling is relevant in the mental health counseling field. However, there is
limited research available pertaining to counselors’ training, experience, and
competencies to provide appropriate and effective grief counseling (Ober et al., 2012).
Breen (2010) conducted a study using grounded theory to find out what are some
of the recommendations for incorporating contemporary understandings into policy and
practices for grief counselors. Breen concluded grief counseling could be harmful to
clients if the counselor is not competent in grief counseling. Breen suggested future
research needs to be conducted for grief education and training for counselors. Breen
aligns with Ober et al. (2012) in which the authors noted the importance for counselors to
seek grief education and training to be competent grief counselors.
Gamino and Ritter (2012) conducted a historical literature review on what it takes
to sensitively and effectively counsel grieving clients. The narrative study concluded
grief counselors must manage their own death anxiety in order to be effective in grief
counseling. The authors stated future research needs to be conducted on the training and
education of counselors in regards to competency in working with grieving clients
(Gamino & Ritter, 2012). Gamino and Ritter align with Ober et al. (2012) in that the
authors all noted that specialized skills in grief counseling are needed to assist in
managing clients’ issues related to dying, death, grief, and bereavement issues.
This study in addition helps to fill the gap in the literature and provide counseling
program leaders and accreditation leaders with research-based information that better

25
informs their decisions about this component of the core curriculum of their counseling
programs. The insight shared with the counseling profession through the results of this
study should help bridge the gap in the literature and promote positive changes to the
curriculum coursework of CACREP-accredited Master’s counseling programs.
Specifically, for CACREP standards to include a thorough discussion of the theories and
skills in grief counseling to assist client’s needs and counseling demands.
Summary
In this quantitative research study, I explored Master’s-level counseling students’
self-assessment of competency in grief education and training in CACREP-accredited
counseling programs. Studying the self reported perceptions of Master students’ level of
competency in grief education and training has many potential benefits for the counseling
profession. For example these benefits may include, increased self-awareness in one’s
perceived competencies in grief counseling, increased ethical behavior in obtaining grief
education and training to promote counseling competencies, increased positive change
for clients seeking counseling for grief related issues, and reduced harm to clients that
counselors serve. The mental health counseling profession ethically values counselor
competency in order to do no harm to the clients we serve; however, there are no core
education and training requirements in grief counseling in CACREP counseling programs
to date.

26
In Chapter 2, the literature and search strategies used for this study in regards to
grief education and training competency development in counseling students are
discussed. In addition, a detailed review of the theoretical foundation used in this study
and the rational on why the choice of this theory. Lastly, grief strategies and interventions
were discussed. In Chapter 3, information on the research design and rationale,
methodology, population sample, data analysis plan, and ethical procedures were
discussed. In Chapter 4, the results of the study and statistical evidence that lead to the
conclusions of this study are provided. In Chapter 5, an interpretation of the findings,
limitations of the study, recommendations for future research to be conducted, and
present implications of positive social change are presented.

27
Chapter 2: Literature Review
Everyone experiences grief sometime within his or her lifetime (Humphrey,
2009). According to Ober et al. (2012), with the aging baby boomers the need for grief
counseling will be on the rise as this population experiences loss. In addition, many U.S.
war veterans are returning home from the Middle East with mental health issues related
to grief and loss (Marshall, 2006; Papa et al., 2008). Ober et al. (2012) stated not all
counselors are adequately trained or comfortable in providing grief counseling.
According to Breen (2010), grief is a common experience in life, and grieving
individuals seek counseling to assist them in coping with their loss. In addition, Breen
stated there is a misalignment between contemporary grief research and grief counseling
practices. This may limit intervention effectiveness in grief counseling. Breen conducted
a qualitative research study and used grounded theory. Breen used semistructured
interviews with 19 grief counselors to gain an understanding on their current practices of
grief counseling. Breen provided some recommendations for incorporating contemporary
understandings into policy and practice for grief counselors. The results indicated a need
for grief education and training. Breen noted grief counseling could be damaging to
clients if counselors are not competent, and suggested future research needs to be
conducted on the limited or lack of grief education and training in counselors’ formal
studies. The information may provide a compelling rationale for the inclusion of grief
content in the curricula of counseling programs.

28
Ober et al. (2012) stated that grief is prevalent in counseling; however, little is
known about counselors’ training, experience, and competencies to provide effective
care. Ober et al. suggested that future research needs to be conducted to investigate
current training on grief counseling across counselor education programs.
In this chapter I include a review of the literature and the search strategies used,
including the databases, key terms, and theoretical foundation. Furthermore, I present the
variables and the value they have added to the mental health counseling field, including
key issues pertaining to grief education and training in the mental health counseling
profession and the effects of grief counseling on clients. Lastly, I discuss implications for
future direction in the mental health counseling field.
Literature Search Strategy
To find literature for this study, I conducted multiple searches using the following
databases and search engines: Academic Search Complete, Dissertations and Theses via
ProQuest, ERIC, Google Scholar, Health & Psychosocial Instruments, Health Science: A
SAGE full text collection, Mental Measurements Yearbook, ProQuest Central,
PsycARTICLES, SocINDEX, PsycINFO, PsycTESTS, SAGE full text collection, SAGE
Premier, and Walden University Dissertations and Theses via ProQuest in which I
accessed the data bases using Walden University Library resources. The key search
terms and combinations of search terms included master’s-level counseling students
education and training, CACREP standards education and training, counselor education

29
and training, grief counselors education and training, grief and loss education and
training, grief counseling, grief competency, grief counseling competencies, grief, loss,
professionals’ experiences of grief counseling, grief issues, and grief therapy. I also used
these terms: psychodynamic theory, attachment theory, continuing bond theory, stage or
task theories, meaning making theories, and the dual process model of grief.
The focus of this literature review was identify relevant papers published within
the past 10 years. However, I also used earlier research that provided the foundation on
the topics and theories in this dissertation. The types of literature I used were from peer-
reviewed journals, theses and dissertations, and books. There has been an increase in
current research in the area of grief education and training in the mental health counseling
field over the last 10 years (Ober et al., 2012). The available research relating to mental
health counselors’ grief education and training is included in this dissertation.
Theoretical Foundation
In the mental health profession, there are several theories that can be used to
address an individual’s experience of grief and used in grief counseling. In the following
pages I will give a brief overview of several of the different theories of grief. It is
important to understand the disparities which exist between the different theories which
are evident in the most recent research. The theories that I will discuss include
psychodynamic theory, attachment theory, continuing bond theory, stage or task theories,
meaning making theory, and the dual process model of grief.

30
Psychodynamic Theory
In Western culture, the beginning of modern grief theory started with Freud
(Granek, 2010). Freud (1917/1963) discussed the normal response to loss in Mourning
and Melancholia. Freud suggested a typical reaction to loss is for the bereaved person to
withdraw their emotions and attention from the loved one who died and refocus their
emotions and attentions in other areas of their life – i.e., on something or someone else.
He felt that one must detach his or her feelings and emotions from the deceased in order
to process grief. Freud suggested ongoing emotional relations with the deceased were
pathological grieving (see, e.g., Granek, 2010).
Lindemann (1944) spurred a transformational change in the understanding of
acute grief, because he suggested grief is a psychological response. According to
Lindemann, acute grief seems to be a normal reaction to a distressing situation.
Lindemann conducted and published an empirical study on bereaved individuals in which
he interviewed 101 recently bereaved individuals and documented their grieving process
using a scientific and objective approach. Lindemann suggested the results of the study
provided representation of what the grieving process entailed, listing normal and
abnormal grief symptoms, and patterns of grieving. He stated professionals in the mental
health field should aid their clients in grief work.
Lindemann (1944) suggested that counselors aid grieving clients by helping them
work through grief by confronting the reality of their loss and attending to the loss

31
instead of isolating oneself from the loss experience (Cicchetti, 2010). He suggested by
helping the client to process feelings associated with the loss of the loved one, the client,
can effectively work towards readjustment to life without the deceased and form new
relationships (Granek, 2010; Lindemann, 1944).
Attachment Theory
Bowlby (1980) explained attachment theory as being based upon the tendency of
humans to develop affection bonds or attachments with their caregivers, as a result of
consistent availability, closeness, security, and the ability to meet their survival needs. In
Bowlby’s earlier work, he explained attachment theory in the context of a child’s
attachment to its mother (primary caregiver) and the disruption due to separation,
deprivation, or bereavement (Bowlby, 1958; Carr & Cortina, 2011). Bowlby (1980)
discussed attachment theory in regards to the loss of a loved one in his book Attachment
and Loss. He explained that during the course of healthy development, a person who is
responsive to another person’s needs enables that person to develop affection bonds and
attachment. He described attachment as a psychological connectedness between a child
and a parent and later between an adult with another adult. When the attachment ends
because of a separation or death; the remaining person then grieves.
Bowlby (1980) wrote about his observations and how individuals responded to
the loss of a loved one over weeks, months, and sometimes years through four phases.
Bowlby noted an individual may move back and forth between any two of the phases.

32
The four phases that Bowlby discussed are numbing, yearning and searching for the
deceased person, disorganization and despair, and a greater or lesser degree of
reorganization.
In the first phase referred to as the numbing phase, an individual may feel
stunned, in disbelief, tense, or apprehensive as an immediate reaction to the news of a
loved one has died (Bowlby, 1980). Bowlby noted the numbing phase could last a few
hours or up to a week. The griever may or may not have outburst of intense distress or
anger which may be intermittent during this phase (Bowlby, 1980).
In the second phase, also referred to as the phase of yearning and searching for
the deceased, an individual may be restless, preoccupied with thoughts of the deceased,
pining for the deceased loved one, feeling distressed, or tearful sobbing (Bowlby, 1980).
Bowlby noted the phase of yearning and searching for the deceased could start within a
few hours of receiving the news of the death of a loved one or could start after a few
days. Bowlby noted the yearning and searching phase could last for months and
sometimes even for years depending on the individual.
In the third phase, also referred to as the phase of disorganization and despair, an
individual may examine how and why the loss happened, be angry at others, eventually
accept the loss in order to reorganize, and move forward in life without the deceased
(Bowlby, 1980). Bowlby noted the phase of disorganization and despair could last for
months and sometimes for years depending on the individual and the responsibilities they

33
now have solely upon them and their situation. Once the bereaved individual recognizes
that they must fill new roles, learn new skills, and are successful the individual becomes
more confident and independent (Bowlby, 1980).
In the fourth phase referred to as the phase of greater or lesser degree of
reorganization, the individual needs to change their old ways of thinking, feeling, and
acting, so they can learn new ways of being in their current life (Bowlby, 1980). Bowlby
noted the phase of greater or lesser degree of reorganization can lasts for years. This
depends on the persistence of relationship with the deceased, children living in the
household or not, duration of grieving, and emotional loneliness of the widowed/widower
(Bowlby, 1980). During this phase, the individual tries to find a redefinition of self to
one’s situation. Bowlby discussed the different phase’s one goes through to process the
responding to the loss of a loved one from emotional responses to emotional detaching
from the deceased loved one through the bereavement experience.
Continuing Bonds Theory
However, Klass, Silverman, and Nickman (1996) countered attachment theory by
suggesting a continuing bonds theory. Klass, Silverman, and Nickman suggested
individuals may not disconnect from the deceased, but stay connected with the deceased
loved one. Continuing bonds theory is different than attachment theory in which the
individual continues a feeling of connection with their deceased loved one. While also
acknowledging the differences from when their loved one was alive when compared to

34
the present without the loved one (Hastings, 2012). Even though the relationship is
altered between the living and the deceased, continuing bonds will be reconfigured and
an emotional relationship will remain between the living person/people and the deceased
(Hastings, 2012).
Field, Gao, and Paderna (2005) expanded upon continuing bond theory by adding
the attachment theory perspective in coping with bereavement. They examined the
grieving process pertaining to different factors of the relationship between the survivor
and the deceased, and investigated the effect of the death of a spouse or child, culture,
and religion on the type of continuing bonds within the attachment theory framework. As
for the continuing bonds theory, it continues to evolve within the field of bereavement
research.
Stage or Task Theories
In grief counseling literature, stage or task theories are discussed and often
reference the most familiar theoretical works of Elisabeth Kubler-Ross. Kubler-Ross
(1969) provided leadership for the American death and dying movement with the
emphasis on the different stages of anticipation of death. Kubler-Ross discussed the need
to openly address issues surrounding an impending death for the dying person with their
friends and family. Parkes (2013) noted Kubler-Ross’ work focuses on the “stages of
grief” in reference to dying patients (p.95). Kubler-Ross wrote about her experiences
working with terminally ill patients in her book called On Death and Dying. According to

35
Kubler-Ross, there are five stages of anticipating death: denial, anger, bargaining,
depression, and acceptance.
In the first stage, denial the individual denies whatever the information is being
told to them using the defense the information cannot be true (Kubler-Ross, 1969).
According to Kubler-Ross, denial often functions as a buffer after receiving the shocking
news. She stated individuals used denial as a temporary defense before moving to the
second stage.
In the second stage, anger the individual is no longer able to maintain denial any
longer; their feelings are replaced with anger (Kubler-Ross, 1969). According to Kubler-
Ross, during this stage the individual may ask “Why me?” Sometimes the anger feelings
may be present, because, before the life event the individual may have controlled many
different parts of their life and now they have lost the control of things that they use to be
able to control, hence, anger (Kubler-Ross, 1969).
In the third stage, bargaining an attempt to postpone what is going to happen;
prize offering for good behavior (Kubler-Ross, 1969). For example, a promise will be
made by the individual that they will not ask for more if this one postponement is
granted. During this stage of bargaining, usually the individual will bargain with their
higher power belief system.
In the fourth stage, depression the individual can no longer deny their terminal
illness diagnosis and will have a sense of great loss as they begin to understand

36
impending death (Kubler-Ross, 1969). During this stage, the individual starts to grieve
the way things used to be and start to feel sad, fear, regret, and uncertainty. According to
Kubler-Ross, when the individual starts to feel those emotions the individual is beginning
to accept the situation and starts to move towards the fifth stage.
In the fifth stage, acceptance the individual begins to come to terms with their
terminal illness and inevitable future death (Kubler-Ross, 1969). Individuals enter this
stage often before the loved ones they leave behind, who go through their own stages of
grief. During this stage, the individual with the terminal illness starts to have a calm view,
stable mindset, and accepts that they need to prepare for the inevitable (Kubler-Ross,
1969).
Kubler-Ross’ stage theory was developed with individuals facing death and not
empirically tested, however, the stages have been referenced and applied to grief and
bereavement in counseling texts, journal articles, and in course content (Hashim, Mei-Li,
& Guan, 2013; Humphrey, 2009; Parkes, 2013). In Kubler-Ross’ book On Grief and
Grieving, she discussed how her theory had previously been applied in a rigid manner.
Readers often seemed to assume that people needed to complete the stages of grief in
sequential order for one to achieve a healthy resolution with one’s loss (Kubler-Ross &
Kessler, 2005). On the contrary, she argued the stages were a guideline to the grief
experience and one can move within the different stages individually or with an overlap
of the different stages (Kubler-Ross & Kessler, 2005).

37
Furthermore, other theorists in the field have developed their interpretations of
stage/task theories of grief (Rando, 1995; Westberg, 1971; Worden, 2009) and have been
criticized along with Kubler-Ross for the ridged application of the stages/task with clients
in which limits a counselor’s ability to understand the client’s individual and unique
grieving experience (Servaty-Seib, 2004). Richardson (2007) argued the stages/task are
not rigid and exclusive, therefore, one’s feelings in response to the loss such as grief can
change in intensity or fluctuate in various stages/task and in any order. The rigid
application of stages or task theories should be avoided, because it limits the practitioner
in understanding the client’s individual and unique response to their loss of their loved
one.
Meaning Making Theory
In contrast to stage or task theories of grief, the meaning making theory stresses
the importance for the client to find meaning and make sense of the loss (Holland &
Neimeyer, 2010; Neimeyer, 2001). Processing one’s grief is a continual process and does
not end with a specific stage or task. Furthermore, the meaning the client makes is unique
to their loss due to their experiences with the deceased, including age, personality,
gender, and the events which led up to the loved ones death (Holland & Neimeyer, 2010;
Neimeyer, 2001).
In a recent study, D’Amore and Scarciotta (2011) examined meaning making
theory with families confronted with multiple losses. According to D’Amore and

38
Scarciotta, unresolved grief within a family limits sharing emotions in which results in
poor family meaning making of the loss. Furthermore, they suggested meaning making
theory can be used to recreate, review, and reconstruct the family bonds around the
experienced losses by finding meaning and making sense of the loss.
Dual Process Model of Grief
Strobe and Schut (1999) introduced the dual process model to gain an
understanding on how to help individuals with grief. They used trauma/stress,
attachment, and grief theories to understand the individual’s stressors as loss-orientated
or restoration-oriented. Loss-orientated refers to the loss of the physical relationship with
the deceased. Restoration-oriented refers to decrease of financial resources and an
increase in responsibilities without the loved one around to provide assistance.
According to the authors, bereaved individuals move back and forth processing the loss
of their loved one emotionally or using problem solving techniques/action orientated
(oscillation). The back and forth processing is a healthy way to cope with the loss of a
loved one, because it allows the individual to experience their loss at different times
(Strobe & Schut, 1999).
Richardson (2007) used the Strobe and Schut (1999) dual process model in grief
counseling. According to Richardson, the dual process model endorses the bereavement
process as a dynamic struggle between the pain due to a disability or loss of job (loss-
oriented) and recovery (restoration-oriented). The dual process model of grief suggests

39
bereaved individuals should alternate between directly working on one’s loss
(confrontation) and taking a break from (avoidance) the process when appropriate
(Richardson, 2007). The dual process model of grief results indicated significant
associations between oscillation and well-being. Findings from other studies demonstrate
the oscillation on grieving promotes positive change (Richardson, 2007).
Educating and Training Counselors in Grief Counseling
Education and training of counselors are consistently being explored and evolve
as the population being served faced different issues and challenges. Therefore, it is
important to investigate current education and training of counselors in grief counseling.
Moreover, it is important to investigate competence in grief counseling and the
contributing factors as to the limited education and training in modern grief theories and
effective interventions. Current studies indicated counseling programs do not require
education and training requirements pertaining to death, dying, grief, or loss related
issues (Breen, 2010; CACREP, 2009 Standards; Horn, Crews, & Harrawood, 2012; Ober
et al., 2012; Werth & Crow, 2009).
According to Breen (2010), grief and loss education and training course work are
not required in most counseling programs (Dougherty Horn et al., 2012; Ober et al.,
2012). However, Breen argued that counselors should be educated and trained in grief
counseling to assist clients with loss and grief issues. The American Academy of Grief
Counseling and The Association for Death Education and Counseling are organizations

40
that professional counselors can obtain credentialing in grief counseling, however, the
majority of professional counselors do not complete the continuing educational
requirements or take the exam to obtain the special credentialing certification (Breen,
2010; Ober et al., 2012).
In a recent study, Ober et al. (2012) used a simple random sample of 1,000
participants selected from a Midwestern listing of 6,919 state board LPCs and surveyed
them on “Grief Counseling Competencies, personal experiences with grief, and
professional training and experience on grief” (p.152). According to Ober et al., they had
a survey return rate of 37.4% (374 respondents). However, surveys with significant
responses missing were removed and not used in the study. Therefore, there were 369
usable surveys (Ober et al., 2012).
According to Ober et al. (2012), 21.1% (n = 76) identified up to 3 years of
experience as licensed professional counselors, 29.1% (n = 105) reported 4 to 9 years of
experience, 26.0% (n = 94) indicated 10 to 20 years of experience, and 23.8% (n = 86)
reported as having more than 20 years of experience. The majority of the participants in
the Ober et al. study were female (77%) and European American (92.7%) with a reported
age range between 25-78 years old and an average age of 48 years old. Ober et al.
reported that a small percentage of the participants identified as African American
(3.8%), as multiracial (1.6%), Latino (0.8%), Asian American (0.3%), or Native
American (0.3%).

41
Additionally, Ober et al. (2012) reported 58.4% (190 respondents) reported they
did not complete any courses pertaining to grief education and training. However, 73.2%
(254 respondents) reported they did complete at least one course on grief. Moreover,
69.4% (247 respondents) reported they completed some education and training hours on
grief counseling. Furthermore, 91% (334 respondents) agreed with a statement that
education and training in grief counseling is needed and should be made a requirement
(Ober et al., 2012).
In the demographic survey, Ober et al. (2012) asked licensed professional
counselor participants to report their familiarity with various grief counseling theories in
which most 42.8% (158 respondents) recognized (the not empirical) stage theory by
Kubler-Ross (1969). However, 49.6% (183 respondents) reported only some familiarity
with the Kubler-Ross stage theory. Furthermore, Worden (2009) task theory and
Neimeyer (2001) meaning making theory were known by 28.2% (104 respondents) and
25.5% (94 respondents) had some familiarity with the aforementioned two theories.
However, 40% (148 and 159 respondents) reported that they were not familiar with task
or meaning making theories. In addition, Ober et al. noted 15.4% (57 respondents) were
least familiar with Strobe and Schut (1999) dual-process model and 14.9% (55
respondents) were least familiar with (Klass, 2001) continuing bonds theory. However,
Ober et al. noted 48% (177 respondents) were not familiar at all with Strobe and Schut

42
(1999) dual-process model and 52.8% (195 respondents) were not familiar at all with
(Klass, 2001) continuing bonds theory.
According to Ober et al. (2012), the findings noted that the LPC participants that
obtained education or training in grief counseling rated themselves more competent in
comparison to the LPC participants that did not complete any education or training in
grief counseling. Furthermore, Ober et al. suggested in the implications and directions for
future research section that an investigation into current grief counseling education and
training should be completed across all counseling programs. Moreover, Ober et al. stated
the information obtained from such a study could provide much needed information to
start establishing standards and competencies for education and training in grief
counseling in the mental health counseling field. In addition, establishing standards and
competencies for education and training in grief counseling will enable counselors to
ethically and effectively assist the growing population of clients with their presenting
needs pertaining to loss, grief, bereavement, death, and dying (Breen, 2010; CACREP,
2009 Standards; Gamino & Ritter, 2012; Horn, Crews, & Harrawood, 2012; Ober et al.,
2012; Werth & Crow, 2009).
Core Skills, Behaviors, and Qualities of Counselors
There is substantial literature published on core skills, qualities, and behaviors
that are important for all practicing counselors (e.g., Aladag, Yaka, & Koc, 2014; Cory &
Cory, 2007; Hansen, 2009; Smith & Moss, 2009; Swank, Lambie, & Witta, 2012). Some

43
of the noted basic core counseling skills are (a) listening, (b) empathy, (c) genuiness, (d)
unconditional positive regard, (e) focusing the session, (f) boundaries, (g) concreteness,
(h) open-ended questions, (i) counselor self-disclosure, (j) interpretation, and (k)
information giving and removing obstacles to promote change (Cory & Cory, 2007;
Hansen, 2009; Smith & Moss, 2009; Swank, Lambie, & Witta, 2012). Gamino and Ritter
(2012) suggested the counselor’s ability to empathetically listen and understand the
client’s unique grieving experience promotes the counselor and client’s successful
working relationship. In addition to basic core counseling skills, the counselor’s
enthusiasm, confidence, and the belief that the client is able to change are all very
important to build a therapeutic working relationship between the counselor and client
(Bernard & Goodyear, 2009).
In addition to core skills and behaviors, there are noted qualities needed in
counselors such as acceptance, confidence, empathy, emotional stability, fairness,
flexibility, genuiness, and interest in people, open-mindedness, and sensitivity
(Aladag,Yaka, &Koc, 2014; Cory & Cory, 2007; Hansen, 2009; Smith & Moss, 2009;
Swank, Lambie, & Witta, 2012). Roos (2002) as cited in Gamino and Ritter (2012) stated
the six qualities grief counselors need are (a) ability to maintain focus, (b) consistency
with goal-directed work, (c) rational confidence, (d) perceptive and empathetic accuracy,
(e) respectful acknowledgement to the client’s pain, and (f) competency in timely and
parsimonious interventions.

44
The counselor’s interactions with the client are a powerful tool in the helping
relationship to promote positive change (Janesick, 2011). Clients are likely to reach their
goals when a good working rapport exists in the client-counselor working relationship
(Bernard & Good year, 2009). Understanding the core skills, behaviors, and qualities that
are necessary for counselors to have are very important to be effective in the counseling
field.
Knowledge, Assessment, and Treatment Skills
Counselors are required to have knowledge, assessment, and treatment skills
specific in the area in which they are practicing, and are to ensure competence in their
work and protect the client from harm (ACA, 2014). According to Gamino and Ritter
(2012), a grief counselor’s work should be based on thorough knowledge on modern grief
theories, valid assessments, and effective treatment interventions to ethically and
effectively help clients with their presenting issues pertaining to grief and loss.
Charkow (2002) developed a survey on grief counseling competencies. Her grief
counseling competencies survey is divided into subscales: (a) personal competencies, (b)
conceptual skills and knowledge, (c) assessment skills, and (d) treatment skills. The
personal competencies subscale measures a counselor’s thoughts and feelings about grief,
along with counselor’s overall wellness (Ober et al., 2012). The personal competencies
subscale topics concern self-care, humor, personal philosophy, spirituality, and
counselor’s attitude on loss (Ober et al., 2012). The conceptual skills and knowledge

45
subscale topics assess one’s knowledge pertaining to normal grief and complicated grief,
effective and ineffective coping skills, knowledge of grief theories, and understanding of
end-of-life/death. The assessment skills subscale topics assess the counselor’s knowledge
in assessing the client for unresolved losses, suicide assessment; assess spirituality,
cultural grief experiences, and medical referrals for treatment. The treatment skills
subscale assess the counselor’s ability to provide psychoeducational information on loss
and grief issues, provide individual, group, and family grief counseling that focuses on
grief and loss issues, build rapport with clients, use active listening skills with clients so
they feel heard, reframe the client’s loss experience, use creative art therapy counseling,
and explore or cocreate new/old mourning rituals (Ober et al., 2012). The Charkow
survey has been used in pilot study, past research studies by Ober et al. and Smith (2003),
and a modified renamed version by Cicchetti (2010) used in this dissertation. Not only is
it important for grief counselors to have knowledge, assessment, and treatment skills in
grief counseling they also need to be efficient in personal competencies, cultural
competencies, and professional competencies in order to practice ethically and
successfully with grieving clients.
Personal Competence
The Council for Accreditation of Counseling and Related Educational Programs
(CACREP) notes that self-awareness is important and a prerequisite for counselor fitness
(CACREP, 2016). Hansen (2009) suggested the construct for self-awareness are as

46
follows: “(a) the self must exist, (b) this self must be available for introspection, (c) the
self must have an enduring essence, and (d) the self must be able to be represented by
language” (p.186). According to Hansen, “self-awareness is highly valued by the
counseling profession” (p. 186).
Duba and Magenta (2008) highlighted the importance of counselor’s self-
awareness in relation to grief counseling. According to Duba and Magenta, the decision
on whether or not to counsel loss, grief, end-of-life care, decision-making, and
bereavement is an important ethical dilemma for counselors working with individuals,
families, and the aging population. Advance techniques in medical care have assisted
people to live longer (Ober et al., 2012). Furthermore, Duba and Magenta stated the
importance of proper training and education that counseling students and counselors need
in order to assist clients with their presenting issues. Counselors need to be competent
when assisting clients and their families with loss, grief, end-of-life care, decision-
making, and bereavement (ACA, 2014).
Duba and Magenta (2008) suggested different strategies that counseling students
and counselors can do as part of their own self-awareness and reflecting. For example,
counselors and counseling students should go to a funeral or wake. The idea of this action
is to have some exposure to death to assist in the process of desensitization to death
(Duba & Magenta, 2008).

47
Also, Duba and Magenta (2008) suggested that a counseling student should attend
hospice or grief/bereavement support groups and listen to the participants talk about their
concerns, thoughts, and feelings, in order to understand their views. Counselors and
counseling students should process their own personal feelings and thoughts on the
subject of loss, grief, end-of-life care, decision-making, and bereavement (Duba &
Magenta, 2008; Jones, 2010). Counselors and counseling students should also
acknowledge their values and feelings about loss, grief, end-of-life care, decision-
making, euthanasia, and bereavement. Self-awareness and processing one’s feelings will
assist the counselor’s growth and development to ethically and effectively assist one’s
clients (Duba & Magenta, 2008).
Professional Competence
The American Counseling Association (ACA, 2014) “Code of Ethics” Section
C.2. professional competence stated counselors are to practice within their boundaries of
competence based on their education, training, supervised experience, license,
credentials, and professional experience. Moreover, multicultural counseling
competency is a requirement across all mental health counseling specialties (ACA, 2014).
Multicultural counseling philosophy is culture based and the client’s problems may be
external or culturally based. Multicultural counselors understand that the client’s belief
system is important. Therefore, the counselor’s goals are cultural understanding,
awareness of biases and values, and understanding change in oppressive systems. The

48
common techniques used in multicultural counseling are worldview considerations and
self-awareness (Sue & Sue, 2008). However, techniques vary based on client population
and the client's presenting needs (Sue & Sue, 2008). According to Hays (2008), the
applicable aspects that will assist counselors with self-awareness pertaining to
understanding different worldviews, values, and biases. The three elements that are
considered the foundation are compassion, humility, and critical thinking skills - these
will assist in counselor’s work with culturally dissimilar clients (Hays, 2008).
Therefore, it is important to keep an open-mind in order to understand other's
views, beliefs, traditions, and behaviors, especially since people grieve differently
(Humphrey, 2009). In addition, counselors need to be realistic in what they have to offer,
their own limitations, and accepting the contribution of their clients' worldviews and
traditions (Doughty Horn, Crews, & Harrawood, 2013). Counselors should increase
openness, use critical thinking skills to identify and challenge assumptions, influences,
and alternatives of their own beliefs when working with grieving clients (Doughty Horn,
Crews, & Harrawood, 2013). Finally, counselors need to be kind, warm, and
compassionate when communicating with their clients to continuing building a good
working relationship to promote change (Hays, 2008).
Responsibility of CACREP Programs
The vision of CACREP is to promote excellence and to provide leadership
through its accreditation standards by continually improving programs and preparing

49
professionals to provide services and to promote optimal human development (Urofsky,
2013). CACREP accreditation provides recognition that the quality and content of the
program meets the standards set by the profession to reflect the needs of a dynamic,
complex, and diverse society (CACREP, 2016). Students and supervisees enrolled in a
CACREP-accredited program can be assured the appropriate knowledge and skill areas
are included in the program and the program is professionally and financially stable.
Furthermore, graduating from a CACREP-accredited program constitutes an important
credential and distinguishes counselors as having completed a program that meets the
standards of excellence for the profession (CACREP, 2016; Urofsky, 2013).
Counselor Training in CACREP Master’s Programs
The Council for Accreditation of Counseling and Related Educational Programs
(CACREP) is a specialized accrediting body for professional preparation in specific
graduate degree programs within the accredited institution (CACREP, 2016; McGlothlin
& Davis, 2004). There are seven specialized standards noted in the 2016 CACREP
Standards, as follows: (a) addiction counseling, (b) career counseling, (c) clinical mental
health counseling, (d) clinical rehabilitation counseling, (e) college counseling and
student affairs, (f) marriage, couple, and family counseling, and (g) school counseling
(Bobby, 2013; CACREP, 2016). There are well-defined criteria outlining the national
standards and training of skills in which graduate students must be held accountable
(Urofsky, 2013).

50
According to the CACREP standards, training in CACREP master’s-level mental
health counseling accredited programs require a minimum of 60 semester credit hours or
90 quarter credit hours for all students to meet the academic unit requirement (CACREP,
2016). In addition, the master’s-level core coursework must include the following eight
content areas: (a) professional counseling orientation and ethical practice, (b) social and
cultural diversity, (c) human growth and development, (d) career development, (e)
counseling and helping relationships, (f) group counseling and group work, (g)
assessment and testing, and (h) research and program evaluation (CACREP, 2016).
Additionally, students are required to successfully complete supervised practicum
experience with a minimum of 100 clock hours in which 40 of those hours are required to
be direct client service hours. During the supervised practicum experience, the master’s-
level student must obtain one hour of site supervision per week and one and a half hours
of program faculty group supervision per week. Furthermore, after the master’s-level
student successful completes the practicum experience requirements they need to
successfully complete a supervised internship experience of 600 clock hours in which
240 hours must be direct client service hours and leading groups. During the supervised
internship, the master’s-level student must obtain one hour of site supervision per week
and one and a half hours of program faculty group supervision per week (CACREP,
2016).

51
However, the CACREP standards do not mention nor do they require course work
pertaining to loss or grief (Doughty Horn, Crews, & Harrawood, 2013). Eckerd (2009)
and Wass (2004) also noted that loss and grief are not noted in the CACREP standards.
Therefore, this topic may be overlooked in master’s-level counseling education and
training programs (Doughty Horn, Crews, & Harrawood, 2013; Eckerd, 2009; Wass,
2004). Eckerd noted that education on the college level would be useful to assist students
with developing knowledge and skills set to help those with presenting issues due to loss
or grief.
Effectiveness of Grief Counseling
Research results indicated that grief counseling is effective when provided to
individuals who self-referred to obtain help or individuals that are referred by a
professional due to grief symptoms (Gamino, Sewell, Hogan, & Mason, 2009; Currier,
Neimeyer, & Berman, 2008; Schut, Stroebe, van den Bout, & Terheggen, 2001).
Additionally, Jones (2010) noted individuals who receive grief counseling after the loss
of a loved one appear better able to cope with the loss of a loved one compared to
individuals that did not receive services. Furthermore, Jones suggested grief counseling
prior to the death of a loved one could potentially reduce post bereavement care.
Neimeyer and Currier (2009) conducted a meta-analysis of controlled outcome
research on grief therapies. The authors reviewed 48 peer-reviewed published articles and

52
16 unpublished dissertations, totaling 61 outcome studies. The results suggested that grief
therapy can be beneficial in helping people with grief and loss issues.
Education and Training for Counselors to provide Grief Counseling
According to Doughty Horn, Crews, and Harrawood (2013), research is sparse
pertaining to loss and grief education/training in the field of mental health counseling.
Harrawood, Doughty, and Wilde (2011) conducted a qualitative study of master’s
students who were enrolled in a loss and grief course specific to death and dying issues.
The results of the study, the researchers identified three themes the participants reported
and they are (a) increased openness to the constructs of death, (b) better understanding of
one’s own beliefs regarding death, and (c) fear of death decreased (Harrawood, Doughty,
& Wilde, 2011). The results of the themes identified in the study suggested the
participants who took a loss and grief course specifically pertaining to dying and death
issues may be less likely to personalize, project, or impose unexamined beliefs or values
onto the client dealing with loss or grief (Harrawood, Doughty, & Wilde, 2011).
Furthermore, the authors stated due to the themes noted in the study, the participants that
took a class may have less fear when addressing loss, grief, death, and dying issues with
their clients. Furthermore, the findings are consistent with previous studies which
indicated education on grief and loss issues may have a positive influence on counselor’s
comfort level in assisting clients with presenting issues pertaining to grief and loss

53
(Doughty Horn, Crews, & Harrawood, 2013; Ober et al., 2012; Smith-Cumberland, 2006;
Wong, 2009).
Doughty Horn, Crews, and Harrawood (2013) conducted a quantitative study and
sent out a questionnaire to random ACA members to investigate counselor trainees’ and
counselors’ anxiety levels when dealing with loss and grief. The study included 161
participants who attended workshops on grief reported a significant decreased anxiety
levels while working with loss, grief, and death issues with clients. According to Ober et
al. (2012), counselors’ experience and training were predictors pertaining to knowledge;
skills set, and comfort level when working with client’s presenting issues of loss and
grief.
Doughty Horn, Crews, and Harrawood (2013) provided a questionnaire to a list of
random ACA members. The study results noted 135 participants (83.9%) indicated they
did not take loss or grief courses as part of their graduate studies. Currier, Neiymeyer,
and Berman’s (2008) meta-analysis of research study results indicated grief counseling
interventions can help a client with their loss and grief issues. Similarly, the Doughty
Horn, Crews, and Harrawood results indicated the need for counselors’ to have more
exposure to the aforementioned topics and suggested incorporating loss and grief
education and training into core curriculum in CACREP graduate counseling programs.

54
Competency in Grief Counseling
Counselor competence is an important component of our ethical principles
regarding beneficence and nonmaleficence (Gamino & Ritter, 2012). Beneficence means
accomplishing something helpful for the client and/or society by knowing how to address
the presenting issue, promoting mental health, and well-being (ACA, 2014; Gamino &
Ritter, 2012). Nonmaleficence is to avoid actions that can cause harm to the client or the
population one serves through incompetent and ineffective actions (ACA, 2014; Gamino
& Ritter, 2012).
Grief counseling competencies are important and needed in the mental health
counseling field to provide a foundation for all counselors to work from the grief
experience of the counselor and the client and how it impacts the daily living of a
growing society experiencing loss (Ahmed, Wilson, Henriksen Jr., & Jones, 2011).
According to Smith, Klaus, Russel, and Skinner (2009), it is important for counselors to
be educated, trained, and competent in grief counseling, because people will experience
grief sometime during their lifetime. Breen (2010) noted that loss is universal; however,
an individual’s grief experiences are culturally determined and unique.
According to Gamino and Ritter (2012), the importance of professional
competence when working in grief counseling that one should continually strive to attain
professional competence through continuing education and attending workshops to
promote one’s professional growth in obtaining up-to-date knowledge and current skills

55
in grief counseling. Counselors should only practice within the limits and boundaries of
their competencies (ACA, 2014). Competency in grief counseling is important to
culturally, ethically, and effectively assist clients with their presenting grief issues.
According to Schoulte (2011), throughout history cultures have grieved the loss of
a loved one using practices, rituals, and expected roles that people from outside the
culture may not have understood or appreciated. Latino/a American culture will
collaborate with all adult family members about end of life care decisions for a terminally
ill parent. In addition, Latino/a American culture prefers for the dying loved one to be in
the home with friends and family members beside the loved one and with the women as
the caregivers (Schoulte, 2011). Doran and Hansen (2006) conducted a qualitative study
on three Latino/a American families that had lost a child. The results indicated that the
families maintained relationships with their deceased child through “dreams, storytelling,
keepsakes, and a sense of presence, faith-based connections, proximity connections,
rituals, and pictorial remembrances” (Doran & Hansen, 2006, pp 208-209; Schoulte,
2011, p. 14). Moreover, the grieving processes were culturally reasonable for Latino/a
American culture (Schoulte, 2011).
It is common for those identifying with African American culture to gather
together for prayer and meditation to assist the deceased loved one with their transition to
the spirit life and to the afterlife (Schoulte, 2011). African American families prepare
food, clothing, chanting, singing, and prayers to welcome the dead into the spiritual life

56
(Schoulte, 2011). Schoulte noted some African American cultures believe the spirits of
the deceased loved one are actively in touch with the living loved ones (hearing deceased
in dreams or feeling deceased presence). African American Christians view death as a
beginning of a new type of life and not the end. African American children and women
express grief freely and sometimes “falling out” in other terms fainting which is
considered a reasonable emotional response of grief (Schoulte, 2011).
Wellness
Working with client’s that have experienced grief and loss can be emotionally and
mentally draining for a counselor. According to Wester, Trepal, and Myers (2009),
counselor wellness is being (a) mentally, physically, and emotionally stable, (b) self-
aware of any biases or impairments, (c) able to recognize when one is stressed, and (d)
will take appropriate actions to promote well-being. Researchers have noted counselors
that are well themselves are most likely to produce well clients (Skovholt, 2012; Wester,
Trepal, & Myers, 2009; Witmer & Young, 1996). In counseling, the counselor is the
professional instrument; therefore, the counselor must take care of himself or herself to
be able to ethically and effectively assist the client (Janesick, 2011; Skovholt, 2012).
Research has indicated that an impaired or unwell counselor may harm the client
(Skovholt, 2012; Wester, Trepal, & Myers, 2009; Witmer & Young, 1996). With that in
mind, counselors have the responsibility to the profession to take the necessary steps to
promote their own well-being to promote the well-being of the ones they serve.

57
Professional Responsibility
To work ethically and effectively with clients that present with issues pertaining
to loss and grief, counselors need to reflect and be aware how their own loss or grief
experience has affected them. Most people including counselors have experienced some
type of loss or grief in their life, but many never talked to anyone about their experience
(Morgan & Roberts, 2010). Counselors have a responsibility to monitor one’s self and
work through any unresolved issues of loss and grief before working with clients, so, they
do not limit the clients’ grieving process and success (Morgan & Roberts, 2010). With
that being said, it is the responsibility of the counselor to effectively deal with his or her
own loss or grief. Therefore, the counselor can be present to enhance the treatment
effectiveness with their grieving clients – anything else would be unethical.
Ethical Concerns
In the field of professional mental health counseling, there are many ethical
concerns when working with the population one serves. It is important that the counselor
works within and adheres to the ethical codes of the profession to protect the counselor
and the client. The key ethical concerns are those relating to education and training, grief
counseling, and counselor wellness, according to the ethical codes of the ACA, and
American Mental Health Counselors Association (AMHCA).

58
American Counseling Association
The purpose of the ACA “Code of Ethics” is to outline, describe, and provide
direction concerning the ethical behaviors and responsibilities that counselors should
aspire to implement in their practices (ACA, 2014). One ethical issue is to be educated
and trained to provide effective grief counseling. According to the ACA (2014) “Code of
Ethics” section C.2.a. boundaries of competence, counselors should only practice within
their competency in skills based on one’s education, training, experience, and
professional credentials.
According to the ACA (2014) “Code of Ethics” section C.2.b. new specialty
areas of practice, counselors must know the limits of their boundaries and practice within
the limits of their specialty areas after appropriate training, education, and supervised
experience to ensure competence of their work and to protect the client from possible
harm. Assisting clients to adjust to loss and grief require special counseling skills and the
need for grief counselors will be on the rise in the coming years (Ober et al., 2012).
Therefore, an ethical issue is where should grief counselors obtain the appropriate
training, education, and supervised experience since it is not part of the core curriculum
requirements in master’s-level counseling CACREP-accredited programs. According to
Breen (2010), grief counseling is a delicate area of counseling and could be detrimental
or even damaging to a client if the counselor is not competent.

59
Another ethical issue is a counselor’s self-awareness of his or her continuing
education and best practices for working with the diverse population served. The ACA
(2014) “Code of Ethics” section C.2.f. continuing education recognizes the need for
counselors to acquire continuing education and maintain awareness of current
professional and scientific information in the counseling field. An ethical issue is where
should grief counselors obtain continuing education and best practices for working with
diverse populations pertaining to loss and grief work, since it is not part of the core
curriculum requirements in master’s-level CACREP-accredited counseling programs.
Not only do counselors need awareness they also need to promote self-care to be
ethical and effective in their work with others. According to the ACA (2014) “Code of
Ethics” section C.2.g. impairment, it is suggested that counselors should self monitor for
signs of impairment and reframe from providing services when impaired to prevent harm
to clients. Impairment can result from physical, mental, or emotional issues; therefore, it
is important for counselors to engage in self-care to assist in avoiding the ethical issue of
impairment.
American Mental Health Counselors Association
The AMHCA (2010) “Code of Ethics” section C.1. competence stated mental
health counselors must maintain high standards of professional competence in order to
best serve the interest of the client and the population one serves. Additionally,
counselors are to be able to recognize their own boundaries of their areas of competence

60
and the limits of their expertise and provide only the services in which they have
achieved a sufficient level of competence through education, training, or professional
experience. Furthermore, it is important that a counselor maintains knowledge through
continuing education and ongoing education related to professional practice in grief
counseling. Counselors need to be competent in cultural diversity and how the individual
deals with loss or grief through rituals, cultural expectations, and values. Self-awareness
is important for counselors to recognize effectiveness which is dependent on one’s
mental, emotional, and physical health. Therefore, it is ethically important for counselors
take the steps to promote their own well-being to be professional competent with the ones
they serve (AMHCA, 2010). Counselors are professionals and are expected to adhere to
the ethical codes in their professional practice to avoid harming their clients.
Summary
As discussed above, research has shown that the need for grief counseling is on
the rise and that grief counseling is beneficial to clients who experience issues due to loss
and grief. Grief counseling has been shown to be effective; however, grief education and
training are not part of the core curriculum requirements in master’s-level CACREP-
accredited counseling programs. Counselors have ethical responsibilities to be educated
and trained to provide effective grief counseling. In addition, it is the counselor’s ethical
responsibility to know the limits of his or her boundaries of expertise, and to practice
only within those to protect the client from possible harm. Furthermore, it is the

61
counselor’s ethical responsibility to obtain continuing education and to be up-to-date on
best practices for working with diverse populations in reference to their members’
individual unique experiences pertaining to loss and grief issues. In addition, it is
important for counselors to explore and understand their own beliefs and level of comfort
in providing grief counseling to others. The self-reported levels of competency, skills,
and knowledge on the GCCS survey will be used in this study to understand master
students’ self-assessment of competency in grief education and training in CACREP-
accredited counseling programs to assist in closing the gap that exists in the literature. In
Chapter 3, I discuss information on the research design and rationale, methodology,
population sample, data analysis plan, and ethical procedures.

62
Chapter 3: Research Method
The purpose of this study was to examine whether master’s counseling students in
CACREP-accredited programs feel they have been adequately trained in identifying
grieving clients and providing grief counseling to them. The research questions that
guided my research study were adapted from Cicchetti (2010). The research questions are
as follows: How competent do master’s-level counselors view themselves regarding the
education or training they received in grief theories or counseling skills in their
CACREP-accredited studies? How do the demographic variables relate to perceived
grief counseling competency? Controlling for course offerings, what is the relationship
between coursework and perceived grief counseling competency? What is the
relationship between practicum or internship setting and perceived grief counseling
competency? Additionally, I tested related hypotheses, as well.
In this chapter, I restate the purpose of the study, present the research questions,
and provide a rationale for the research design method that I used. I provide the planned
sampling and sampling procedures, instrumentation, data analysis plan, internal and
external validity, and ethical considerations. In addition, I discuss in depth the research
design, procedures, and instrumentation for my study. I conclude the chapter with a
summary.

63
Research Design and Rationale
In this quantitative study, I used a non-experimental, one shot survey comparative
design to investigate the perceptions of master’s students in CACREP-accredited
counseling programs. Data were collected using the GCCS (Cicchetti, 2010) and the
DDS. These instruments were used to measure the counseling students’ self reports of
their perceived competency in education and grief counseling on four sub-scales
(personal competencies, conceptual skills and knowledge, assessment skills, and
treatment skills). The DDS was also used to also collect demographic data on
participants’ gender, age, race, and ethnicity. Information about participants’ coursework
and practicum and internship setting were also recorded. The independent variables
included the demographic variables of gender, age, race, and ethnicity, coursework, and
clinical setting (i.e., practicum or internship setting). The four grief competency sub
scales on the GCCS were the dependent variables, with a covariate of course offering.
The research method and data collection method were both appropriate for my study,
because the methods allow the specific research questions to be answered through the
participants’ responses to the questions on the survey. The instruments were appropriate
for my study, because it allowed the participants’ to provide their perceived competency
through their education or training in grief counseling in which the participants obtained
in their formal coursework in their CACREP counseling program. The survey design was

64
appropriate, because it allowed me to test the hypotheses. Detailed operational definitions
are in Table 1 and Table 2.
Table 1
Operational Definitions of Independent Variables
Demographic variables Included gender, age, race, and ethnicity.
Practicum/Internship Setting Where the participant completed practicum or internship at the
time of data collection and included such setting as
community/mental health setting, school setting, hospital setting,
rehabilitation facility, state agency, or residential setting
(Cicchetti, 2010).
Coursework Did the participant take any courses in grief theories and
interventions and the relationship between courses taken and
grief counseling competency (Cicchetti, 2010, p.61).

65
Table 2
Operational Definitions of Dependent Variables
Personal Competencies Defined by nine items on the GCCS (Cicchetti, 2010) related to
participants’ reported self-care, self-awareness with grief issues,
humor, spirituality, and personal beliefs pertaining to loss and
grief. Sample questions on the GCCS on Personal Competencies
are “I practice personal wellness and self-care” and “I have self-
awareness related to my own grief issues and history” (Cicchetti,
2010, p.60).
Conceptual Skills and
Knowledge
Defined by nine items on the GCCS (Cicchetti, 2010) related to
participants’ reported level of confidence in defining normal
grief, describing effective and ineffective coping skills, and the
ability to apply counseling theories to case conceptualization.
Sample questions on the GCCS on Conceptual Skills and
Knowledge are “I believe that there are no one right way to deal
with grief” and “I can define and articulate the nature and
symptoms of complicated or unresolved grief situations”
(Cicchetti, 2010, p. 60).
Assessment Skills Defined by nine items on the GCCS (Cicchetti, 2010) assessed
participants’ ability to evaluate clients for unresolved losses,
suicide assessments, assess spirituality, recognize cultural
influences, and make appropriate referrals. Sample questions on
the GCCS on Assessment Skills are “I can assess for unresolved
losses that may not be stated as a presenting problem” and “I can
conduct suicide assessments” (Cicchetti, 2010, p. 60).
Treatment Skills Defined by 19 items on the GCCS (Cicchetti, 2010) assessed
participants’ belief in ability to provide psycho-education on grief
and loss issues; facilitate individual, group, or family counseling
sessions on grief; build rapport with clients; use active listening
skills; reframe loss experience; use creative arts in counseling;
and identify cultural influences affecting treatment. Sample
questions on the GCCS on Treatment Skills are “I can facilitate
family grief counseling sessions” and “I can facilitate individual
grief counseling sessions” (Cicchetti, 2010, p. 61).
Covariate: Institutions
offered courses in grief
theories and interventions
Examine the relationship between coursework and perceived
grief counseling competency, measured by the GCCS four sub
scales (Cicchetti, 2010).

66
Research Questions and Hypotheses
The overall general research question adapted from Cicchetti (2010): How
competent do master’s-level counselor’s view themselves regarding the education or
training they received in grief theories or counseling skills in their CACREP-accredited
studies?
RQ1. How do the demographic variables (e.g., gender, age bracket, race, and
ethnicity) relate to perceived grief counseling competency?
H
o
1: There is no significant (α = .05) interaction effect among the demographic
variables and perceived grief counseling competency.
H
1
1: There is a significant interaction effect among the demographic variables
and perceived grief counseling competency.
RQ2. Controlling for course offerings (whether the participant’s course
curriculum offered coursework in grief counseling theories and practice), what is
the relationship between coursework and grief counseling competency?
H
o
2: There is no significant (α = .05) positive relationship between coursework
taken and the four grief counseling competency scales, controlling for course offerings.
H
1
2: There is a significant positive relationship between coursework taken and the
four grief counseling competency scales, controlling for course offerings.
RQ3. What is the relationship between practicum or internship setting and
perceived grief counseling competency?

67
H
o
3: There is no significant (α = .05) relationship for clinical setting and
perceived grief counseling competency.
H
1
3: There is a significant relationship for clinical setting and perceived grief
counseling competency.
Setting and Sample
According to Sandelowski (2007), criterion sampling involves selecting cases in
which there is a predetermined criterion of importance. Criterion sampling can be useful
for identifying and understanding cases that are information rich. Therefore, I used
criterion sampling (Franfort-Nachmias & Nachmias, 2008) to sample the population of
master’s-level students in CACREP-accredited counseling programs. I chose master’s-
level students meeting the criteria of being in their practicum or internship in a CACREP
counseling program as the population instead of LPCs. I wanted to examine the student’s
formal education on grief theories, skills, and grief counseling as opposed to the
experience and training they may receive after completing their counseling program.
Master’s-level counseling students in their practicum or internship were asked to
participate in the study.
Creswell (2009) suggested a survey method uses different sampling procedures
such as single or multi-stage, random, or convenience sampling. According to Frankfort-
Nachmias and Nachmias (2008), “researchers obtain a convenience sample by selecting
whatever sampling units are conveniently available” (p. 168). For this study, I used a

68
convenience sampling (non-probability sampling) procedure to obtain participants. I sent
a letter to program directors of all CACREP-accredited counseling programs listed on the
CACREP website introducing the study and requesting that the program director forward
the invitation to participate and the SurveyMonkey link to their practicum and internship
master’s-level counseling students. One of the limitations of using this sampling
procedure is that the results of this study will not be generalizable to larger populations
(Franfort-Nachmias & Nachmias, 2008).
Electronic surveys sent via e-mail are a way to collect data in descriptive studies
(Creswell, 2009). To obtain the sample size for this study, I used the e-mailing
recommendations of Rovai, Baker, and Ponton (2013). Rovai, Baker, and Ponton stated
e-mail surveys should (a) allow two weeks minimum for collecting electronic surveys,
(b) initiate electronic survey early morning on a business day, (c) follow up contact to
promote positive response rates, (d) provide a short justification of survey promoting the
importance of study, (e) keep the survey short, (f) assure confidentiality or anonymity, (g)
provide periodic reminders, and (h) offer to provide feedback regarding the study.
According to Rovai, Baker, and Ponton, a large sample size with reasonable response
rates are required to minimize nonresponse error. The common criteria for survey
response rates are that higher than 85% is an excellent response rate, 70% to 85% is a
very good response rate, and 60% to 70% is an acceptable response rate. If the response

69
rate of the participants is 60% or higher, nonresponse error is minimized (Rovai, Baker,
& Ponton, 2013).
I sent the e-mail to the program directors in a way to avoid the email being
detected as spam. The letter was written to be appealing and was sent early in the
morning on a business day to all CACREP program directors listed on the CACREP
website. The letter introduced the study and asked them to forward the invitation to
CACREP master’s-level students currently enrolled in their practicum or internship field
experiences. I used an anonymous data collection procedure to eliminate any pressure for
CACREP master’s-level counseling students currently enrolled in their practicum or
internship field experience to participate. I sent an additional email to program directors
after 10 days to promote positive response rates.
A sample size of 225 participants was needed for this study as determined by
using G*Power 3.1.7 software. G*Power 3.1.7 was used to calculate the minimum
number of participants for a medium effect size F test of .25, alpha level of .05, power of
.80, and degrees of freedom of 6. Results indicated that 225 participants would be
required (Faul, Erdfelder, Lang, & Buchner, 2007).
Instrumentation
Demographic Data Sheet
The demographic data sheet included items requesting each participant to
complete information about gender, age, race, ethnicity, and practicum or internship

70
setting (See Appendix C). In addition, participants were asked to complete questions
pertaining to participants’ knowledge attainment on grief theories and interventions in
graduate school. The following questions were adapted from Cicchetti’s (2010) study:
1. Is your program CACREP-accredited?
2. Does the institution you attended offer courses in grief theories?
3. Does the institution you attended offer courses in grief interventions?
4. How many courses did you complete in grief theories?
5. How many courses did you complete in grief interventions?
Grief Counseling Competencies Survey
This study used a modified version with written permission (see Appendix B) of
Cicchetti’s (2010) GCCS to assess for personal grief counseling competencies and skills
and knowledge in grief counseling competencies. The only noted modification in the
GCCS (see Appendix D) used for this study was the removal of the word “disability” in
the section labeled Part II. The word “disability” was removed from the following
numbered questions 12, 14, 15, 23, 25, 30, 31, and 32. The rest of the survey remained
the same as used in Cicchetti’s (2010) study.
Cicchetti (2010) noted he used a modified version of the Death Competency
Survey (DCS; Charkow, 2002). According to Cicchetti, Charkow’s DCS consist of two
parts. The first part of Charkow’s DCS inquired about Personal Competencies using nine
questions. The second part of Charkow’s DCS inquired about Skills and Knowledge

71
Competencies using 36 questions. The two parts of Charkow’s DCS had four
subheadings, as follows: (a) personal competencies, (b) conceptual skills and knowledge,
(c) assessment skills, and (d) treatment skills (Cicchetti, 2010).
Charkow’s (2002) revised version of the DCS, which was renamed GCCS by
Cicchetti (2010) is a 46-item questionnaire survey using a Likert scale to assess the
participant’s personal competencies, conceptual skills and knowledge, assessment skills,
and treatment skills in regards to grief intervention and counseling working with clients
with presenting issues related to loss or grief. The participant chooses the number on the
GCCS which best identifies the participant’s self-reported perceived competency for each
of the questions on the survey. The responses on the survey are 1 (this does not describe
me), 2 (this barely describes me), 3 (this somewhat describes me), 4 (this describes me),
and 5 (this describes me very well) (Cicchetti, 2010).
Part I and II of the GCCS were scored independently. For example, Part I of the
GCCS personal competencies has nine questions using a Likert scale rating 1 through 5
with the higher score representing a greater perceived competency level reported by the
participant in the specific part of the assessment; therefore, the scoring range was 9 to 45
in Part I of the GCCS assessment. Part II of the GCCS skills and knowledge
competencies area of the assessment has 37 questions using a Likert scale rating 1
through 5, therefore, the scoring range was 37 to 185 in that part of the GCCS
assessment. The subscales in Part II of the GCCS skills and knowledge competencies are

72
distributed within three scales as follows: the assessment skills has nine questions,
treatment skills has 19 questions, and conceptual skills and knowledge has nine questions
in the Part II of the GCCS assessment (Cicchetti, 2010).
In adapting the DCS (Charkow, 2002) to create the GCCS, Cicchetti (2010)
removed seven questions specific to death and bereavement. In addition, Cicchetti,
reframed seven questions for the purpose of his study. Cicchetti’s GCCS focused on grief
counselor competencies and were not specific to death and bereavement. For example,
one of the focused questions on death were changed as follows: “I have experienced the
death(s) of a family member and can verbalize my own grief process, to: I have
experienced loss and can verbalize my own grief process” (Cicchetti, 2010, p. 67).
Charkow (2002) contacted 34 experts in grief counseling to develop the DCS. Of
the 34 contacted experts in grief counseling, 27 of them provided feedback and ratings on
the DCS. The definition for expert was noted as an individual with “at least 5 years of
experience in grief counseling, completed three individual surveys regarding (a)
characteristics important for grief counselors to possess, (b) content to be included in
courses/lectures on grief, and (c) general competence” (Cicchetti, 2010, p. 67). The
results were the instrument was used in a pilot study, refined, and used in Charkow’s
(2002) dissertation as the instrument DCS (Cicchetti, 2010).

73
Validity and Reliability
According to Etchegaray and Fischer (2010), researchers place importance on
validity to ensure the inferences made from the design and measurement used are
meaningful, appropriate, and useful, it measures what it claims to measure, and important
decisions can be made from the information obtained. Frankfort-Nacmias and Nacmias
(2008) stated content validity is determined by the degree to which the questions, tasks,
or items on an instrument are representative of the universe of behavior the instrument
was designed to sample.
As discussed by Charkow (2002) and Cicchetti (2010), a demographically-diverse
group of 27 grief experts rated and provided comments on the importance of the included
competency items and the efficacy of the modified Delphi procedure to determine
competency items. The individuals in this group of experts reported expertise in grief
counseling including clinical, research, and educator roles. All experts reported a
minimum of 5 years of experience in grief counseling activities, and 20 of the 27 reported
more than 10 years of experience in the field in grief counseling activities. The terminal
degrees of the individuals in the group of 27 included 14 experts with Ph.D. degrees, 12
experts with Master’s degrees, and 1 expert with an Educational Specialist degree.
Eighteen of the experts were female and 9 were male, and were regionally diverse within
United States. The professional fields represented by the experts included counseling,
counseling education, social work, psychology, family studies, and thanatology. Half (13

74
of the 27) of the experts reported holding certification in grief counseling, grief therapy,
or death education, and in the modified Delphi study, there were 15 expert participants in
the final survey iteration (Charkow, 2002). Content validity was indicated by 14 of the
15 (93. 3%) experts which agreed the included competency items in the survey
adequately or completely addressed the characteristics and the competencies required for
grief counseling (Cicchetti, 2010; Charkow, 2002).
The original instrument (the Death Counseling Scale) has been determined to
have a Cronbach alpha (α) of .87, indicating it is a reliable instrument (Charkow 2002).
Subscales of the instrument lie within the range .79 ≤ α ≤ .94. Specifically, the personal
competency subscale has α = .79, the conceptual skills and knowledge subscale has α =
.92, the assessment skills subscale has α = .87, treatment skills subscale has α = .94, and
the professional skills subscale has α = .83 (Charkow, 2002). Charkow reported a
correlation between DCS and Burgen’s Coping with Death Scale of г = .73, suggested
concurrent validity. Cicchetti (2010) reported the Grief Counseling Competency Scale is
also a reliable instrument with a Cronbach alpha value for the personal competency
subscale of α = .79 and for the skills and knowledge subscale of α = .97. Cicchetti
reported the 3 subscales of the skills and knowledge subscale have Cronbach alphas of
conceptual skills and knowledge subscale (α = .52), assessment skills subscale (α = .60),
and treatment skills subscale (α = .60).

75
Cicchetti (2010) sent the GCCS to two experts in rehabilitation counseling field,
and one grief studies expert to make sure the GCCS was appropriate for his study.
Cicchetti reported he wanted to obtain feedback on the questions in the GCCS in relation
to loss and grief for individuals with disabilities. Cicchetti stated experts in his study
were defined as professionals in the field who had at least five years of teaching
experience in grief theories or interventions in a CACREP master’s-level counseling
program or in a CORE master’s-level rehabilitation counseling program. In addition, the
experts in Cicchetti study also had at least five years of clinical counseling experience
working with clients with presenting grief issues or clients with rehabilitation presenting
issues.
Cicchetti (2010) sent the GCCS and the DCS surveys, information on content
validity and reliability, and the first three chapters of his study to the three experts to
analyze the GCCS and to determine if it was pertinent to the study. The grief counseling
expert suggested adding the question, “I can listen in a non-judgmental way to stories that
clients tell about their losses” (Cicchetti, 2010, p. 69). After Cicchetti incorporated the
feedback, the revised GCCS was sent back out to the three experts, along with the DCS
survey and the information on content validity and reliability, and the research questions
for the final review. The three experts concluded the GCCS survey was pertinent for the
study (Cicchetti, 2010).

76
I sent the GCCS and the DCS surveys, information on content validity and
reliability, and the first three chapters of this study to four experts to analyze the GCCS
and to determine if it was pertinent to the study. The four experts concluded the GCCS
survey was pertinent for the study. The experts had at least five years of clinical
counseling experience working with clients with presenting grief issues.
Data and Collection Procedures
I began data collection began shortly after I received the approval notice from
Walden University’s Institutional Review Board (IRB) for Ethical Standards in Research
(see Appendix A). I recruited the participants by writing e-mail invitations to CACREP-
accredited master’s-level counseling program directors listed on the CACREP website
and asked them to please forward the invitation to CACREP master’s-level students
currently enrolled in their practicum or internship counseling field experience (See
Appendix E). The invitation to participate via e-mail provided the criterion required of
participants to participate in the study and it also provided a link which allowed the
participant to enter the entry page of the survey. The entry page had information about
the study including overview and background, including procedures, voluntary
commitment to participate in the study, benefits and risks of participating in the study,
information on zero compensation, confidentiality, contact information, and statement on
consent (see Appendix F). After the participants had reviewed the implied consent on the

77
entry page, participants were directed to enter the survey, verify consent, and complete
the Demographic Data Sheet (see Appendix C), and the GCCS survey (see Appendix D).
Following the participant’s completion of the DDS and the GCCS survey, the
participant received a debriefing statement form (see Appendix G). The debriefing
statement was used to express gratitude for the participant’s participation, shared
information about how to contact the researcher if needed, reiterated the voluntary
participation in the study, reviewed informed consent information, discussed future
requirements for the study, provided counseling services resources, and shared the study
overview. To increase the response rate for participants, I used the recommendation of
Rovai, Baker, and Ponton (2013) as discussed above. I used MonkeySurvey, which uses
secure encryption technology to ensure confidentiality. After the completion of the study,
data was downloaded to SPSS on a password protected computer.
Data Analysis
Descriptive statistics were calculated (frequency, percent, mean, standard
deviation, and range) to examine the data from the survey. Data from the survey was
analyzed in order to answer the overall general research question adapted from (Cicchetti,
2010): How competent do master’s-level counselors view themselves regarding the
education or training they received in grief theories or grief counseling skills in their
CACREP-accredited studies?

78
RQ1. How do the demographic variables (e.g., gender, age bracket, race, and
ethnicity) relate to perceived grief counseling competency?
H
o
1: There is no significant (α = .05) interaction effect among the demographic
variables and perceived grief counseling competency.
H
1
1: There is a significant interaction effect among the demographic variables
and perceived grief counseling competency.
This question was investigated using a 4-way MANOVA with demographic
variables (gender, age bracket, race, and ethnicity) as independent variables and the four
grief competency sub scales on the GCCS are the dependent variables. The first
demographic variable gender examined for differences on perceived grief counseling
competencies on the GCCS survey. The next demographic variable age examined as a
function of perceived grief counseling competencies on the GCCS survey. The last two
demographic variables race and ethnicity examined for differences on perceived grief
counseling competencies on the GCCS survey.
RQ2. Controlling for course offerings (whether the participant’s course
curriculum offered coursework in grief counseling theories and practice), what is the
relationship between coursework and grief counseling competency?
H
o
2: There is no significant (α = .05) positive relationship between coursework
taken and the four grief counseling competency scales, controlling for course offerings.

79
H
1
2: There is a significant positive relationship between coursework taken and the
four grief counseling competency scales, controlling for course offerings.
This question was investigated using a MANCOVA where the independent
variable is coursework; the four grief competency sub scales on the GCCS are the
dependent variables, and the covariate is course offering. This analysis examined the
relationship between course work taken and the four grief competency sub scales on the
GCCS survey.
RQ3. What is the relationship between practicum or internship setting and
perceived grief counseling competency?
H
o
3: There is no significant (α = .05) relationship for clinical setting and
perceived grief counseling competency.
H
1
3: There is a significant relationship for clinical setting and perceived grief
counseling competency.
This question was investigated using a MANOVA whereas the independent
variable is practicum or internship setting and the four grief competency sub scales on the
GCCS are the dependent variables. This analysis examined the relationship between
practicum or internship setting and perceived grief counseling competencies on the
GCCS survey.
The assumptions of MANOVA are the same for MANCOVA (Rovai, Baker, &
Ponton, 2013). These include that observations are independent and the sample is without

80
any pattern. MANOVA and MANCOVA assume the dependent variables are continuous
or scale variables and independent variables are categorical. However, the MANCOVA
covariates can be continuous, ordinal, or dichotomous (Rovai, Baker, & Ponton, 2013).
Absence of multicollinearity assumptions of MANOVA and MANCOVA
indicates that the dependent variables are not correlated to each other (Rovai, Baker, &
Ponton, 2013). According to Tabachnick and Fidell (2012) no correlation should be
above r = .90. In addition, the assumptions of MANOVA and MANCOVA are
multivariate normality is the dependent variable is normally distributed in the data and
homogeneity of variance is equal between groups. The one additional assumption made
in the MANCOVA that is not in the MANOVA is the relationship between covariate and
dependent variables. Choosing what covariate to use and assessing if an existing
statistical relationship between covariate and dependent variables using a correlation
analysis (Rovai, Baker, & Ponton, 2013).
The assumption of homogeneity of variance can be evaluated using the Levene’s
test of equality of variance (Rovai, Baker, & Ponton, 2013). The Levene’s test of equality
of variance is used to examine if the variance between IV groups are equal. If the
Levene’s test shows non-significant values this indicates equal variance between groups.
The MANCOVA assumptions test homogeneity of regression is important to use
when including a covariate (Rovai, Baker, & Ponton, 2013). Homogeneity of regression
assumes the interaction of the IV by the covariate is not significant. However, slopes

81
relating to the covariate to the DV are equal across all levels. For example, for each level
of IV, the slope of the prediction of the DV from covariate must be equal (Rovai, Baker,
& Ponton, 2013).
Results shared with dissertation committee, Walden University, possible future
publication article, sharing a summary of the results with participants, and professionals
in the mental health field.
Limitations
The threats to internal validity in using the non-experimental, one shot survey
research design is important to discuss on how they may affect this study (Creswell,
2009). However, the threats to internal validity are not a concern for this study. Threats to
internal validity would be (a) history, (b) maturation, (c) regression, (d) mortality, (e)
diffusion of treatment, (f) compensatory/resentful demoralization, (g) compensatory
rivalry, (h) testing, and (i) instrumentation (Creswell, 2009). The participants in this study
were asked to complete a one-time survey online with no interaction and no lapse of time
between participation, therefore, reducing the internal validity threats pertaining to (a)
history, (b) maturation, (c) mortality, (d) diffusion of treatment, (e)
compensatory/resentful demoralization, (f) compensatory rivalry, and (g) testing.
Furthermore, the participants volunteered anonymously and no information was known
about the participants which reduced the internal validity threat of regression (Creswell,
2009). The instruments that were used for this study are the same instruments used for all

82
participants (no changes), with the same written instructions provided at the beginning of
the study to all, therefore, reducing the internal validity threat of instrumentation
(Creswell, 2009).
The threats to external validity that do apply to this study are (a) interaction of
selection and treatment, (b) interaction of setting and treatment, and (c) interaction of
history and treatment (Creswell, 2009). Due to the recruitment criteria of the participants
in this study, generalizability was limited to CACREP-accredited master’s-level
counseling students. Therefore, the findings cannot be generalized to the larger
population or other populations. Additionally, future research during different times of
counseling student’s development may be appropriate. Moreover, replication of this study
at a later time may be useful to determine if the results are the same in both studies.
Obtaining the sample through written request to Program Directors of CACREP
counseling programs was reasonable, since previous researchers used this method
(Cicchetti, 2010; Creswell, 2009; Dillman et al., 2009). According to previous
researchers the response rate for online surveys remains low still today (Cicchetti, 2010;
Creswell, 2009; Dillman et al., 2009). For example, if one does not have emails for the
population of potential participants it would be difficult to send a request to participate in
an email survey. Additionally, response to participate may be low, because participants
may have difficulty sharing that they may have a deficit in grief education and training,
even though the survey design is designed to keep the participants identity anonymous.

83
Limits of confidentiality, anonymity, ethical concerns, and availability of counseling
services were addressed in the consent and debriefing forms of this study.
Ethical Considerations
There are many ethical considerations when working with human participants in a
research study. I made sure the participants understood the risk of participating in this
study, obtained consent, and provided clear guidelines about the purpose of this study and
how to obtain follow-up information if the participant desired. Participants were
informed and information concerning the intent of this study was provided. Information
provided will be kept confidential except for the information obtained on the surveys
which was used in this study. The participants of the study are not members of a
vulnerable population by IRB definition; therefore, no additional ethical considerations
are needed to protect human participants in this study. Before any data collection began,
the IRB application was completed and submitted, reviewed, and approved by Walden
University.
The participants for this study were Master’s-level students in CACREP-
accredited counseling programs currently enrolled in their Practicum or Internship field
experience, who have completed all of their required program courses of study, and who
volunteered to participate after they had been contacted through email via their program
director at their university. I provided a link in the email inviting participants to
voluntarily participate in the study, if they so desired. The first document the participants

84
reviewed pertained to the study information. This information included (a) implied
consent, (b) purpose of the study, (c) procedures, (d) voluntary participation of the study,
(e) benefits and possible risk, (f) confidentiality, and (g) researcher’s contact information.
The consent clearly stated that participation was voluntary and can be withdrawn at any
time. Once participants chose to voluntarily participate in the study they were direct to
the SurveyMonkey link. Clicking on the link implied consent and the survey began.
In order for the participants to remain anonymous, I did not request names and no
personal information was collected in this study. Upon completion of the study, I
downloaded the participant’s responses to a password protected computer using SPSS
software. In SurveyMonkey, I deleted participant’s responses from storage after the data
were downloaded.
Summary
The purpose of this study was to examine whether master’s-level counseling
students in CACREP counseling programs report they have been trained to identify and
work with clients who are experiencing grief related issues from a loss. I used both
MANOVA and MANCOVA analyses. For example, research question 1 investigated
using a 4-way MANOVA with demographic variables (gender, age bracket, race, and
ethnicity) as independent variables and the four grief competency sub scales on the
GCCS are the dependent variables. The first demographic variable gender examined for
differences on perceived grief counseling competencies on the GCCS survey. The next

85
demographic variable age examined as a function of perceived grief counseling
competencies on the GCCS survey. The last two demographic variables race and
ethnicity examined for differences on perceived grief counseling competencies on the
GCCS survey. Research question 2 investigated using a MANCOVA where the
independent variable is coursework; the four grief competency sub scales on the GCCS
are the dependent variables, and the covariate is course offering (whether the
participant’s course curriculum offered coursework in grief counseling theories and
practice). This examined the relationship between course work taken and the four grief
competency sub scales on the GCCS survey. Research question 3 investigated using a
MANOVA whereas the independent variable is practicum or internship setting and the
four grief competency sub scales on the GCCS are the dependent variables. This
examined the relationship between practicum or internship setting and perceived grief
counseling competencies on the GCCS survey.
This study was one of the first to examine CACREP requirements for master’s-
level counseling students which may be deficient in their education and training in grief
theories and interventions. The study will benefit CACREP counseling programs by
examining accreditation standards of programs by requiring course requirements in grief
theories and interventions for master’s-level counseling student in order to meet the
populations growing service needs. There may be a need for CACREP counseling

86
programs to expand current requirements of master’s counseling programs and develop
core curriculum requirements to be included on grief theories and interventions.

87
Chapter 4: Results
The purpose of this quantitative study was to examine whether CACREP-
accredited master’s counseling students in training perceive they have been adequately
trained in identifying clients’ presenting grief issues and in providing grief counseling to
clients in need. The purpose of this study was to examine the question: How competent
do master’s-level counselors view themselves regarding the education or training they
received in grief theories or counseling skills in their CACREP-accredited studies?
RQ1. How do the demographic variables (e.g., gender, age bracket, race, and
ethnicity) relate to perceived grief counseling competency?
H
o
1: There is no significant (α = .05) interaction effect among the demographic
variables and perceived grief counseling competency.
H
1
1: There is a significant interaction effect among the demographic variables
and perceived grief counseling competency.
RQ2. Controlling for course offerings (whether the participant’s course
curriculum offered coursework in grief counseling theories and practice), what is
the relationship between coursework and grief counseling competency?
H
o
2: There is no significant (α = .05) positive relationship between coursework
taken and the four grief counseling competency scales, controlling for course offerings.
H
1
2: There is a significant positive relationship between coursework taken and the
four grief counseling competency scales, controlling for course offerings.

88
RQ3. What is the relationship between practicum or internship setting and
perceived grief counseling competency?
H
o
3: There is no significant (α = .05) relationship for clinical setting and
perceived grief counseling competency.
H
1
3: There is a significant relationship for clinical setting and perceived grief
counseling competency.
Upon the approval of the IRB application, implementation, and the data collection
occurred over 40 days. In this chapter, I discuss the purpose, research questions, and
hypotheses. First, I discuss data collection, recruitment of participants, response rates,
demographic and descriptive characteristics. The results of analysis are presented
pertaining to the evaluation of statistical assumptions, results pertaining to each
hypothesis, and information regarding the covariate. Lastly, I included a summary to
answer the research questions based on the results.
Data Collection
The survey was sent via email to program directors and to program designees, in
lieu of a director of CACREP-accredited counseling programs that were listed on the
CACREP website. I followed the mailing recommendation design of Dillman et al.
(2009) to promote response rate. Specifically, on Day 1, the invitation to participate in
the study and the survey were sent to CACREP accredited program directors. On Day 10,

89
an additional request to participate in the study and to complete the survey was sent. On
Day 20, final requests to participate in the study and to complete the survey were sent.
The survey invitation was sent the fourth week of January 2016 and data
collection was completed in the last week of February 2016. On Days 1, 10, and 20 (see
Appendix E), the survey invitation to participate was sent, including thank you response
emails. Program directors or program designees of CACREP-accredited counseling
programs were asked to forward the survey invitation to their master’s-level students
enrolled in their practica or internships via blind carbon copy. The summary of program
directors’ or their designees’ contacted as follow:
• Three hundred fifteen program directors or program designees received
the survey.
• Seven did not have valid e-mail addresses and therefore were not included.
• Seven had automatic response that they were on sabbatical.
• Fourteen had automatic response that they were out of office for travel.
• Four program directors or program designees reported that their college or
university required IRB approval for the survey to be distributed.
• Seven program directors or program designees were unavailable but
provided another contact name, to which an e-mail was sent.

90
• Two program directors or program designees stated the e-mail to
participate in survey was sent to their colleagues in the department to
distribute to students as per their discretion.
• Twenty-two responded that the e-mail was sent to their students or posted
on listserv.
The survey invitation provided detailed instructions to participants who were
interested in participating in the study and to click the “next” button to begin their review
of the consent form. Participants who continued to the survey from the consent form
provided implied consent ensuring anonymity. Participants were able to cease voluntary
participation at any time. The final sample size was 153 total respondents, of whom 123
answered all questions.
Sample Demographics
I used convenience sampling at CACREP-accredited institutions, in addition to
criterion sampling techniques to ensure that participants were master’s-level counseling
students enrolled in their practicum or internship experience. I selected CACREP-
accredited master’s-level counseling programs to provide a unified level of standards and
expectations in the counseling field. Of the 153 participants who responded to the survey,
all met my criteria, but only 123 participants completed all required responses to the
study. Participants were informed in the Study Information “if there is a question that you
choose not to answer, you may skip the question”. After participants consented to the

91
study (see Appendix E), they completed the DDS and GCCS (Cicchetti, 2010) (see
Appendices C and D). After completing both instruments, participants received a
debriefing letter (see Appendix F).
Of the 153 master’s-level CACREP-accredited counselor trainees who were in
either their practicum or internship participated in this study, 136 (89.47%) reported
being female, while 16 (10.53%) reported being male, and one participant chose not to
respond. Regarding the demographic questions on ethnicity, 142 (92.81%) identified
themselves as No, not Hispanic, Latino, or Spanish origin, 4 (2.61%) identified
themselves as Yes, Mexican, Mexican American, Chicano, 3 (1.96%) identified
themselves as Yes, Puerto Rican, and 4 (2.61%) identified as Yes, another Hispanic,
Latino, or Spanish origin, however, 0 identified as Cuban. On the demographic questions
regarding race, 126 (82.89%) identified themselves as White, 18 (11.84%) participants
identified themselves as Black, African American, or Negro, 3 (1.97%) identified
themselves as American Indian or Alaska Native, 1 (0.66%) identified them self as
Filipino, 2 (1.32%) identified themselves as Other Asian, 1 (0.66%) identified them self
as Guamanian or Charnorro, 1 (0.66%) identified them self as Other Pacific Islander, and
one chose not to respond. All 153 participants responded to the age bracket question, 47
(30.72%) responded in the age bracket of 18-24 years old, 69 (45.10%) responded in the
age bracket of 25-34 years old, 13 (8.50%) responded in the age bracket of 35-44 years
old, 19 (12.42%) responded in the age bracket of 45-54, and 5 (3.27%) responded in the

92
age bracket of 55 plus years old. Reporting on their practicum or internship setting,
respondents indicated 72 (47.68%) were at Community Mental Health settings, 51
(33.77%) were at School settings, 2 (1.32%) indicated at Hospital settings, 1 (0.66%) at
Rehabilitation setting, 4 (2.65%) indicated at State Agency, 2 (1.32%) at Residential
settings, 19 (12.58%) indicated Other not Specified settings, and 2 (1.32%) of the
participants did not respond.
Of the 153 respondents, 153 reported the program they attended was CACREP-
accredited. The list of CACREP-accredited universities was obtained directly from
CACREP via the CACREP website, verified as current accreditation on the CACREP
website, and noted each university’s department program chair. Twenty-two CACREP-
accredited master’s-level counseling programs responded that the e-mail with the survey
link (study) was sent to their practicum or internship students. Since information
pertaining to which school respondents attended was not obtained, there was no way of
knowing how many students from each school or state participated in the study.
Ninety-nine participants (66%) reported the university they attended did not offer
courses in grief theories, 51participants (34%) reported the university they attended did
offer courses in grief theories, and 3 participants did not respond to the question. Ninety-
five participants (62.91%) reported the university they attended did not offer courses in
grief interventions, 56 participants (37.09%) reported the university they attended did off
courses in grief interventions, and 2 participants did not respond to the question. One

93
hundred and twenty-two participants (80.26%) reported they had not taken any courses in
grief theories, 27 participants (17.76%) reported they had taken one course in grief
theories, 3 participants (1.97%) reported taken two courses in grief theories, and one
participant did not answer the question. One hundred and thirteen participants (76.87%)
reported they did not take any courses in grief interventions, 30 participants (20.41%)
reported they had taken one course in grief interventions, 4 participants (2.72%) reported
they had taken two courses in grief interventions, and 6 participants did not answer the
question. The missing data points are participants’ who did not answer the question.
Participants were informed on the Study Information “if there is a question that you
choose not to answer, you may skip the question”. Participant’s characteristics can be
found in Table 3.

94
Table 3
Participant Descriptives
Variable
Frequency (N)
Mean Median
Mode Std. Deviation
Valid
Missing
What is your gender? 152 1 1.11 1 1 .31
What is your age
bracket?
153 0 2.12 2 2 1.08
Is this person of
Hispanic, Latino, or
Spanish origin?
153 0 1.17 1 1 .71
What is this person’s
race?
152 1 1.47 1 1 1.77
Is your program
CACREP-accredited?
153 0 1.00 1 1 .00
Does the institution you
attend offer courses in
grief theories?
150 3 1.66 2 2 .48
Does the institution you
attend offer courses in
grief interventions?
151 2 1.63 2 2 .48
How many courses did
you complete in grief
theories?
152 1 1.22 1 1 .46
How many courses did
you complete in grief
interventions?
147 6 1.26 1 1 .50
Current
Practicum/Internship
Setting.
151 2 2.31 2 1 2.01

95
Distribution of Data
Descriptive statistics was calculated to examine the data from the survey. Data
from the survey was analyzed in order to answer the overall general research question
adapted from (Cicchetti, 2010): How competent do master’s-level counselors view
themselves regarding the education or training they received in grief theories or grief
counseling skills in their CACREP-accredited studies?
There are nine questions on Section 1 of the GCCS pertaining to personal grief
counseling competencies. The scores for each question ranged from 1: “This does not
describe me,” to 5: “This describes me very well.” The higher total score, the higher
perceived personal grief counseling competency. The total score can range from low of 9
to high of 45.
One hundred and forty participants reported in Section 1 of the GCCS (M =
38.03, SD = 4.34). The median score for this section was 38.5 with a mode score of 40,
with a frequency of 15, and total scores ranging from a low 21 with a frequency of 1, to
high of 45 with frequency of 7 (see Table 4 and Figure 1). The distribution scores were
Kurtosis 1.72 and negatively Skewed -.95, (see Table 5).

96
Table 4
Part 1:
Personal Grief Counseling Competencies Response
Totals
Frequency
Percent
Valid
Percent
Cumulative
Percent
Valid 21.00 1
.7
.7
.7
24.00 1
.7
.7
1.4
25.00 1
.7
.7
2.1
26.00 1
.7
.7
2.9
30.00 2
1.3
1.4
4.3
31.00 1
.7
.7
5.0
32.00 5
3.3
3.6
8.6
33.00 7
4.6
5.0
13.6
34.00 7
4.6
5.0
18.6
35.00 10
6.5
7.1
25.7
36.00 9
5.9
6.4
32.1
37.00 14
9.2
10.0
42.1
38.00 11
7.2
7.9
50.0
39.00 11
7.2
7.9
57.9
40.00 15
9.8
10.7
68.6
41.00 14
9.2
10.0
78.6
42.00 12
7.8
8.6
87.1
43.00 8
5.2
5.7
92.9
44.00 3
2.0
2.1
95.0
45.00 7
4.6
5.0
100.0
Total 140
91.5
100.0
Missing System
13
8.5
Total 153
100
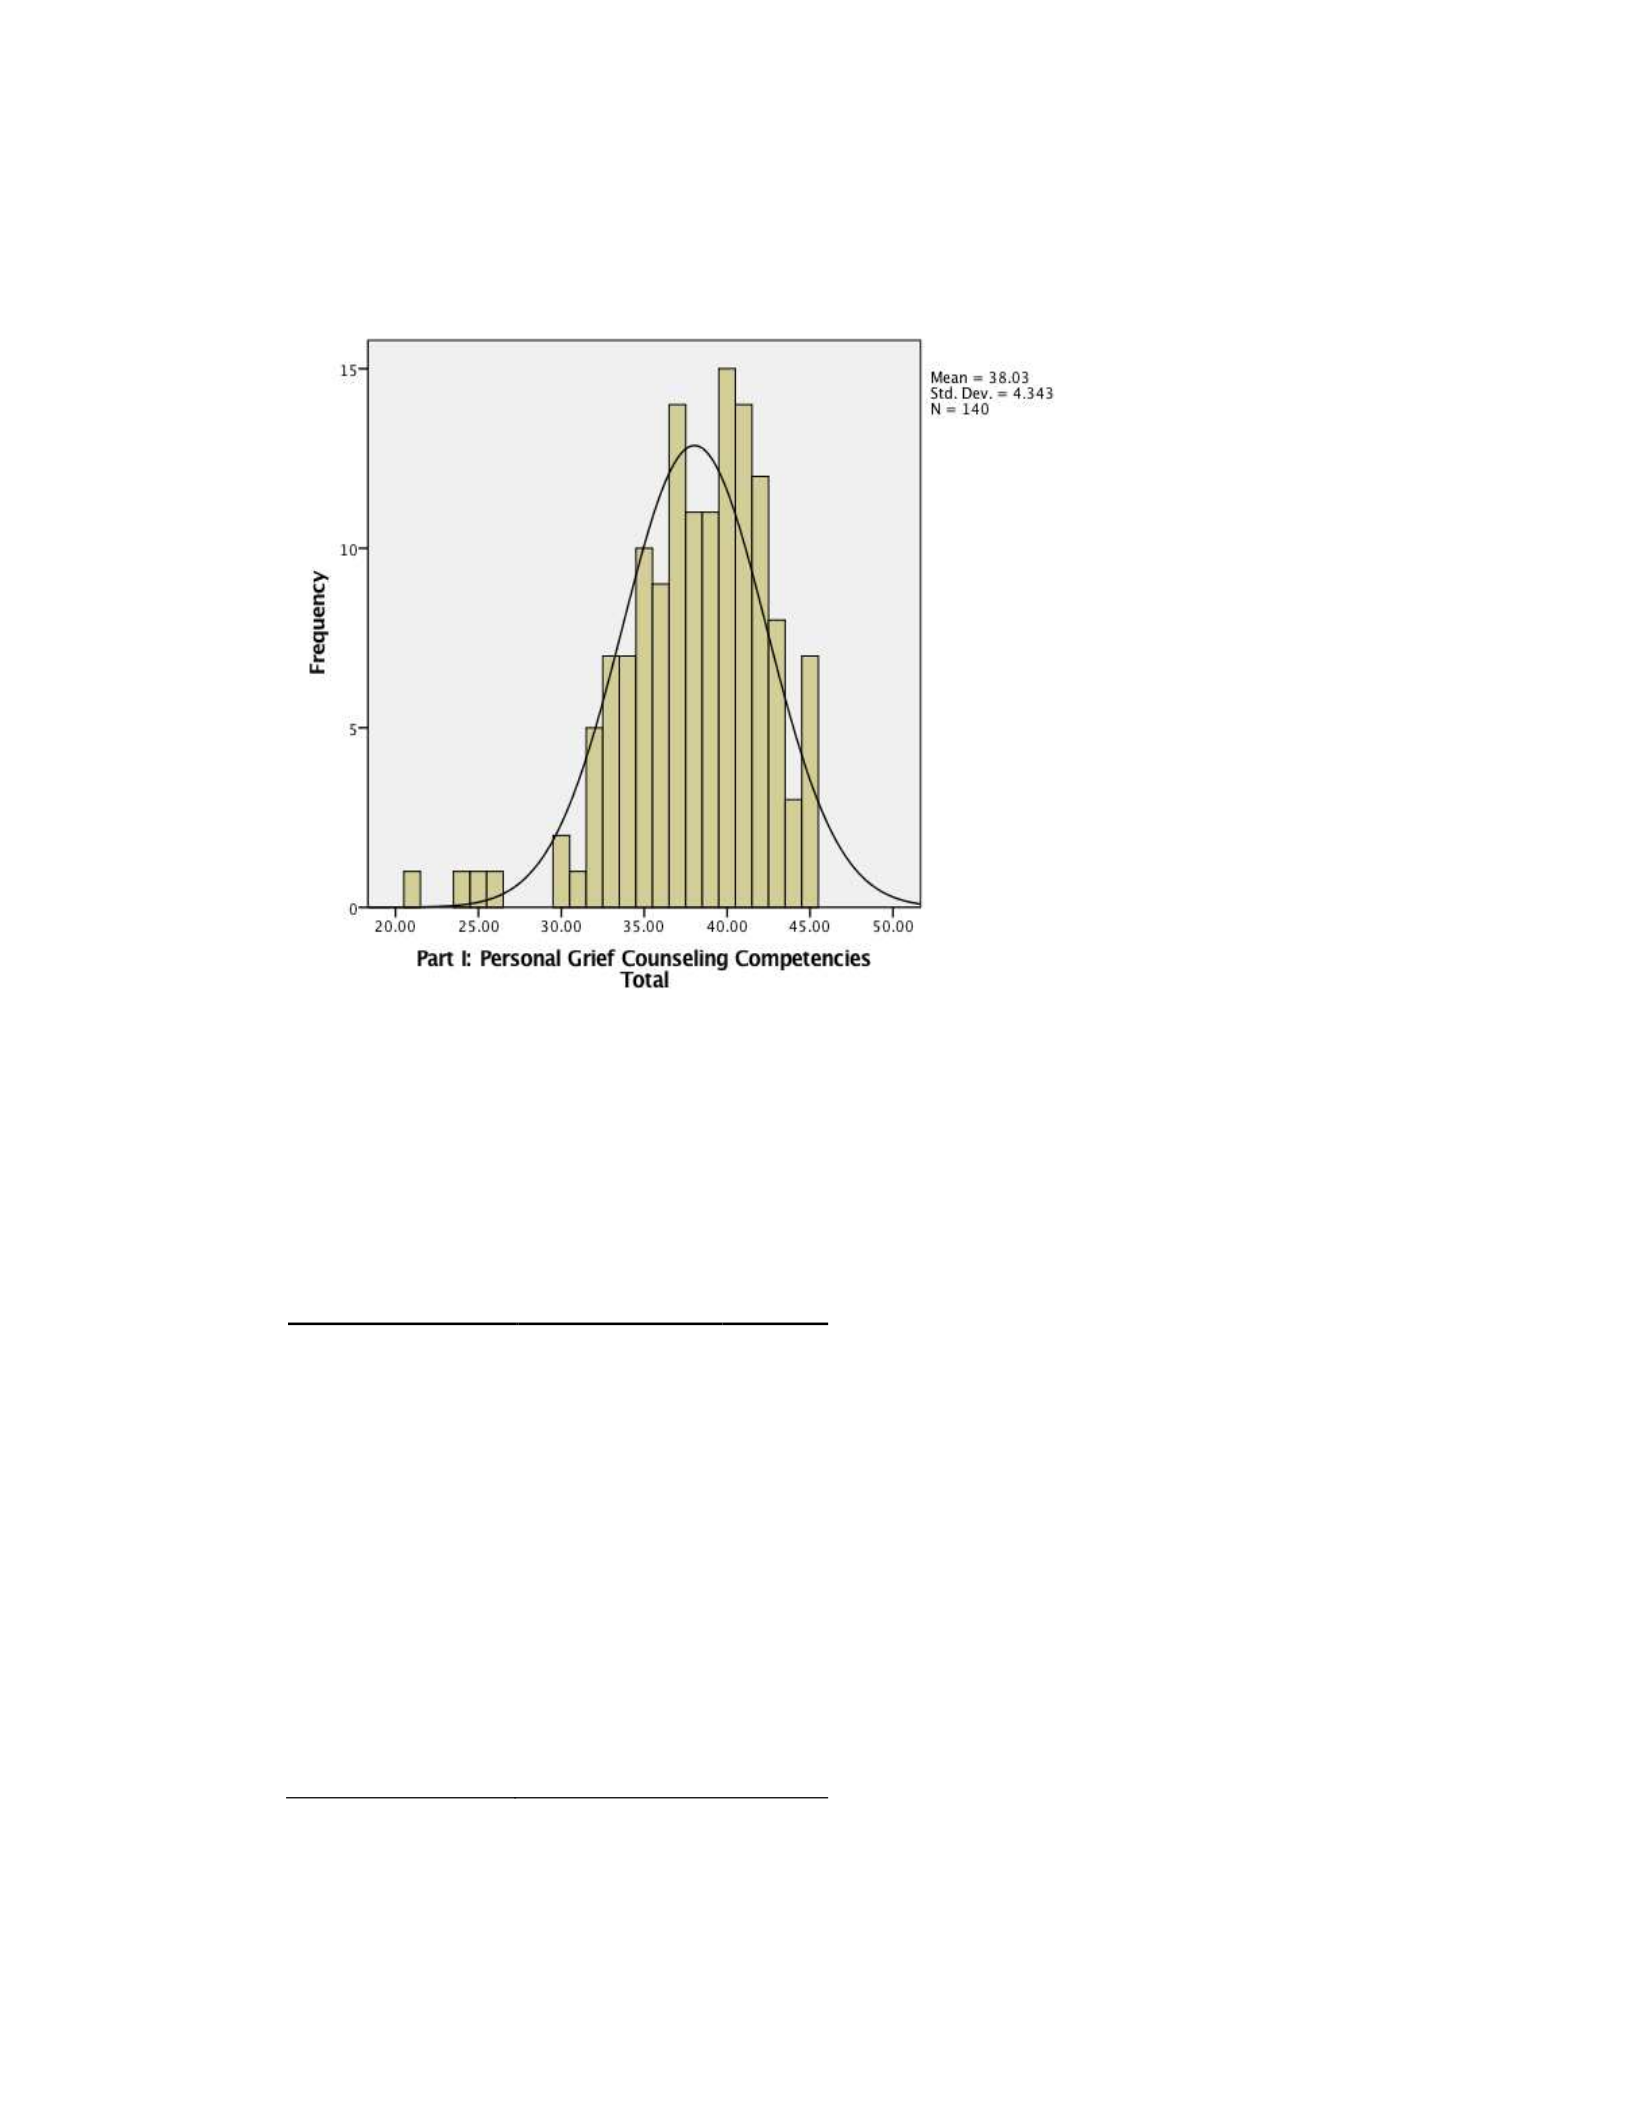
97
Figure 1. Frequency distribution of personal grief counseling competencies
Table 5
Part 1:
Personal Grief Counseling
Competencies Response Totals
N Valid 140
Missing 13
Mean 38.03
Median 38.50
Mode 40.00
Std. Deviation 4.34
Skewness -.95
Kurtosis 1.72
Range 24.00
Minimum 21.00
Maximum 45.00

98
An interquartile range was completed to examine the distribution of 50% of the
scores around median and found scores ranged from 3.9 to 4.6 out of possible 5. This
data shows there was a .7 range of scores on the personal grief counseling competencies
section of the GCCS while the majority of scores were between “this somewhat describes
me” and “this describes me.” Part 1 of the GCCS in reference to personal grief
counseling competencies mean, median, mode, and standard deviation can be found in
Table 6.
99
Table 6
Mean, Median, Mode, and Standard Deviation of Personal Grief Counseling
Competencies
Item
N
Mean Median
Mode
S.D. Valid
Missing
Part 1: Personal Grief Counseling
Competencies
1. I practice personal wellness
and self-care.
140
13
3.9071
4.00
4.00
.79473
2. I have experienced loss and
can verbalize my own grief
process.
140
13
3.8071
4.00
4.00
1.0655
3. I have self-awareness related
to my own grief issues and
history.
140
13
3.9643
4.00
4.00
.90092
4. I believe that grief is a result
of a variety of loss
experiences which include but
are not limited to death.
139
14
4.7050
5.00
5.00
.58301
5. I display empathy,
unconditional positive regard,
and genuineness when talking
with friends and
acquaintances.
140
13
4.5643
5.00
5.00
.60228
6. I view grief as a systemic as
well as an individual
experience.
140
13
4.3500
5.00
5.00
.86436
7. My spirituality is important to
my understanding of grief.
140
13
3.7000
4.00
5.00
1.3233
8. I believe that there is no one
right way to deal with grief.
140
13
4.5071
5.00
5.00
.90161
9. I have a sense of humor. 140
13
4.5571
5.00
5.00
.77061

100
There are 37 questions on Section 2 of the GCCS pertaining to skills and
knowledge of grief counseling competencies. The section has three areas of
concentration: conceptual skills and knowledge, assessment skills, and treatment skills.
conceptual skills and knowledge had nine questions. Assessment had nine questions, and
treatment skills had 19 questions. The scores for each question ranged from 1: “This
does not describe me,” to 5: “This describes me very well.” The higher total score, the
higher perceived skills and knowledge of grief counseling competency. The total score
can range from low of 37 to high of 185.
One hundred and seven participants reported in Section 2 of the GCCS (M =
118.23, SD = 29.352). The median score for this section was 122 with a mode score of
129, with a frequency of 4, and total scores ranging from a low 60 with a frequency of 1,
to high of 182 with frequency of 1 (see Table 7 and Figure 2). The distribution scores
were Kurtosis -.606 and Skewness .049, (see Table 8).

101
Table 7
Part II: Skills and Knowledge Grief Counseling Competency Response Totals
Frequency Percent Valid Percent
Cumulative
Percent
Valid 60.00 1
.7
.9
.9
64.00 1
.7
.9
1.9
65.00 1
.7
.9
2.8
66.00 1
.7
.9
3.7
67.00 1
.7
.9
4.7
70.00 1
.7
.9
5.6
73.00 1
.7
.9
6.5
76.00 2
1.3
1.9
8.4
77.00 2
1.3
1.9
10.3
79.00 1
.7
.9
11.2
81.00 1
.7
.9
12.1
82.00 3
2.0
2.8
15.0
84.00 1
.7
.9
15.9
85.00 1
.7
.9
16.8
86.00 1
.7
.9
17.8
88.00 1
.7
.9
18.7
89.00 2
1.3
1.9
20.6
90.00 2
1.3
1.9
22.4
91.00 1
.7
.9
23.4
92.00 1
.7
.9
24.3
94.00 1
.7
.9
25.2
95.00 1
.7
.9
26.2
98.00 2
1.3
1.9
28.0
99.00 2
1.3
1.9
29.9
102.00 2
1.3
1.9
31.8
103.00 1
.7
.9
32.7
105.00 1
.7
.9
33.6
106.00 2
1.3
1.9
35.5

102
Part II: Skills and Knowledge Grief Counseling Competency Response Totals
Frequency Percent Valid Percent
Cumulative
Percent
109.00 1
.7
.9
36.4
111.00 2
1.3
1.9
38.3
112.00 2
1.3
1.9
40.2
113.00 1
.7
.9
41.1
114.00 3
2.0
2.8
43.9
116.00 1
.7
.9
44.9
117.00 3
2.0
2.8
47.7
119.00 1
.7
.9
48.6
120.00 1
.7
.9
49.5
122.00 3
2.0
2.8
52.3
123.00 1
.7
.9
53.3
124.00 1
.7
.9
54.2
125.00 2
1.3
1.9
56.1
126.00 1
.7
.9
57.0
127.00 3
2.0
2.8
59.8
128.00 1
.7
.9
60.7
129.00 4
2.6
3.7
64.5
130.00 1
.7
.9
65.4
131.00 2
1.3
1.9
67.3
132.00 1
.7
.9
68.2
133.00 2
1.3
1.9
70.1
134.00 2
1.3
1.9
72.0
135.00 1
.7
.9
72.9
138.00 2
1.3
1.9
74.8
139.00 2
1.3
1.9
76.6
140.00 2
1.3
1.9
78.5
141.00 2
1.3
1.9
80.4
142.00 1
.7
.9
81.3
144.00 2
1.3
1.9
83.2
146.00 1
.7
.9
84.1
103
Part II: Skills and Knowledge Grief Counseling Competency Response Totals
Frequency Percent Valid Percent
Cumulative
Percent
147.00 1
.7
.9
85.0
148.00 1
.7
.9
86.0
149.00 1
.7
.9
86.9
150.00 1
.7
.9
87.9
153.00 1
.7
.9
88.8
155.00 1
.7
.9
89.7
156.00 1
.7
.9
90.7
158.00 1
.7
.9
91.6
160.00 1
.7
.9
92.5
164.00 1
.7
.9
93.5
166.00 1
.7
.9
94.4
171.00 1
.7
.9
95.3
174.00 1
.7
.9
96.3
178.00 2
1.3
1.9
98.1
179.00 1
.7
.9
99.1
182.00 1
.7
.9
100.0
Total 107
69.9
100.0
Missing System 46
30.1
Total 153
100.0
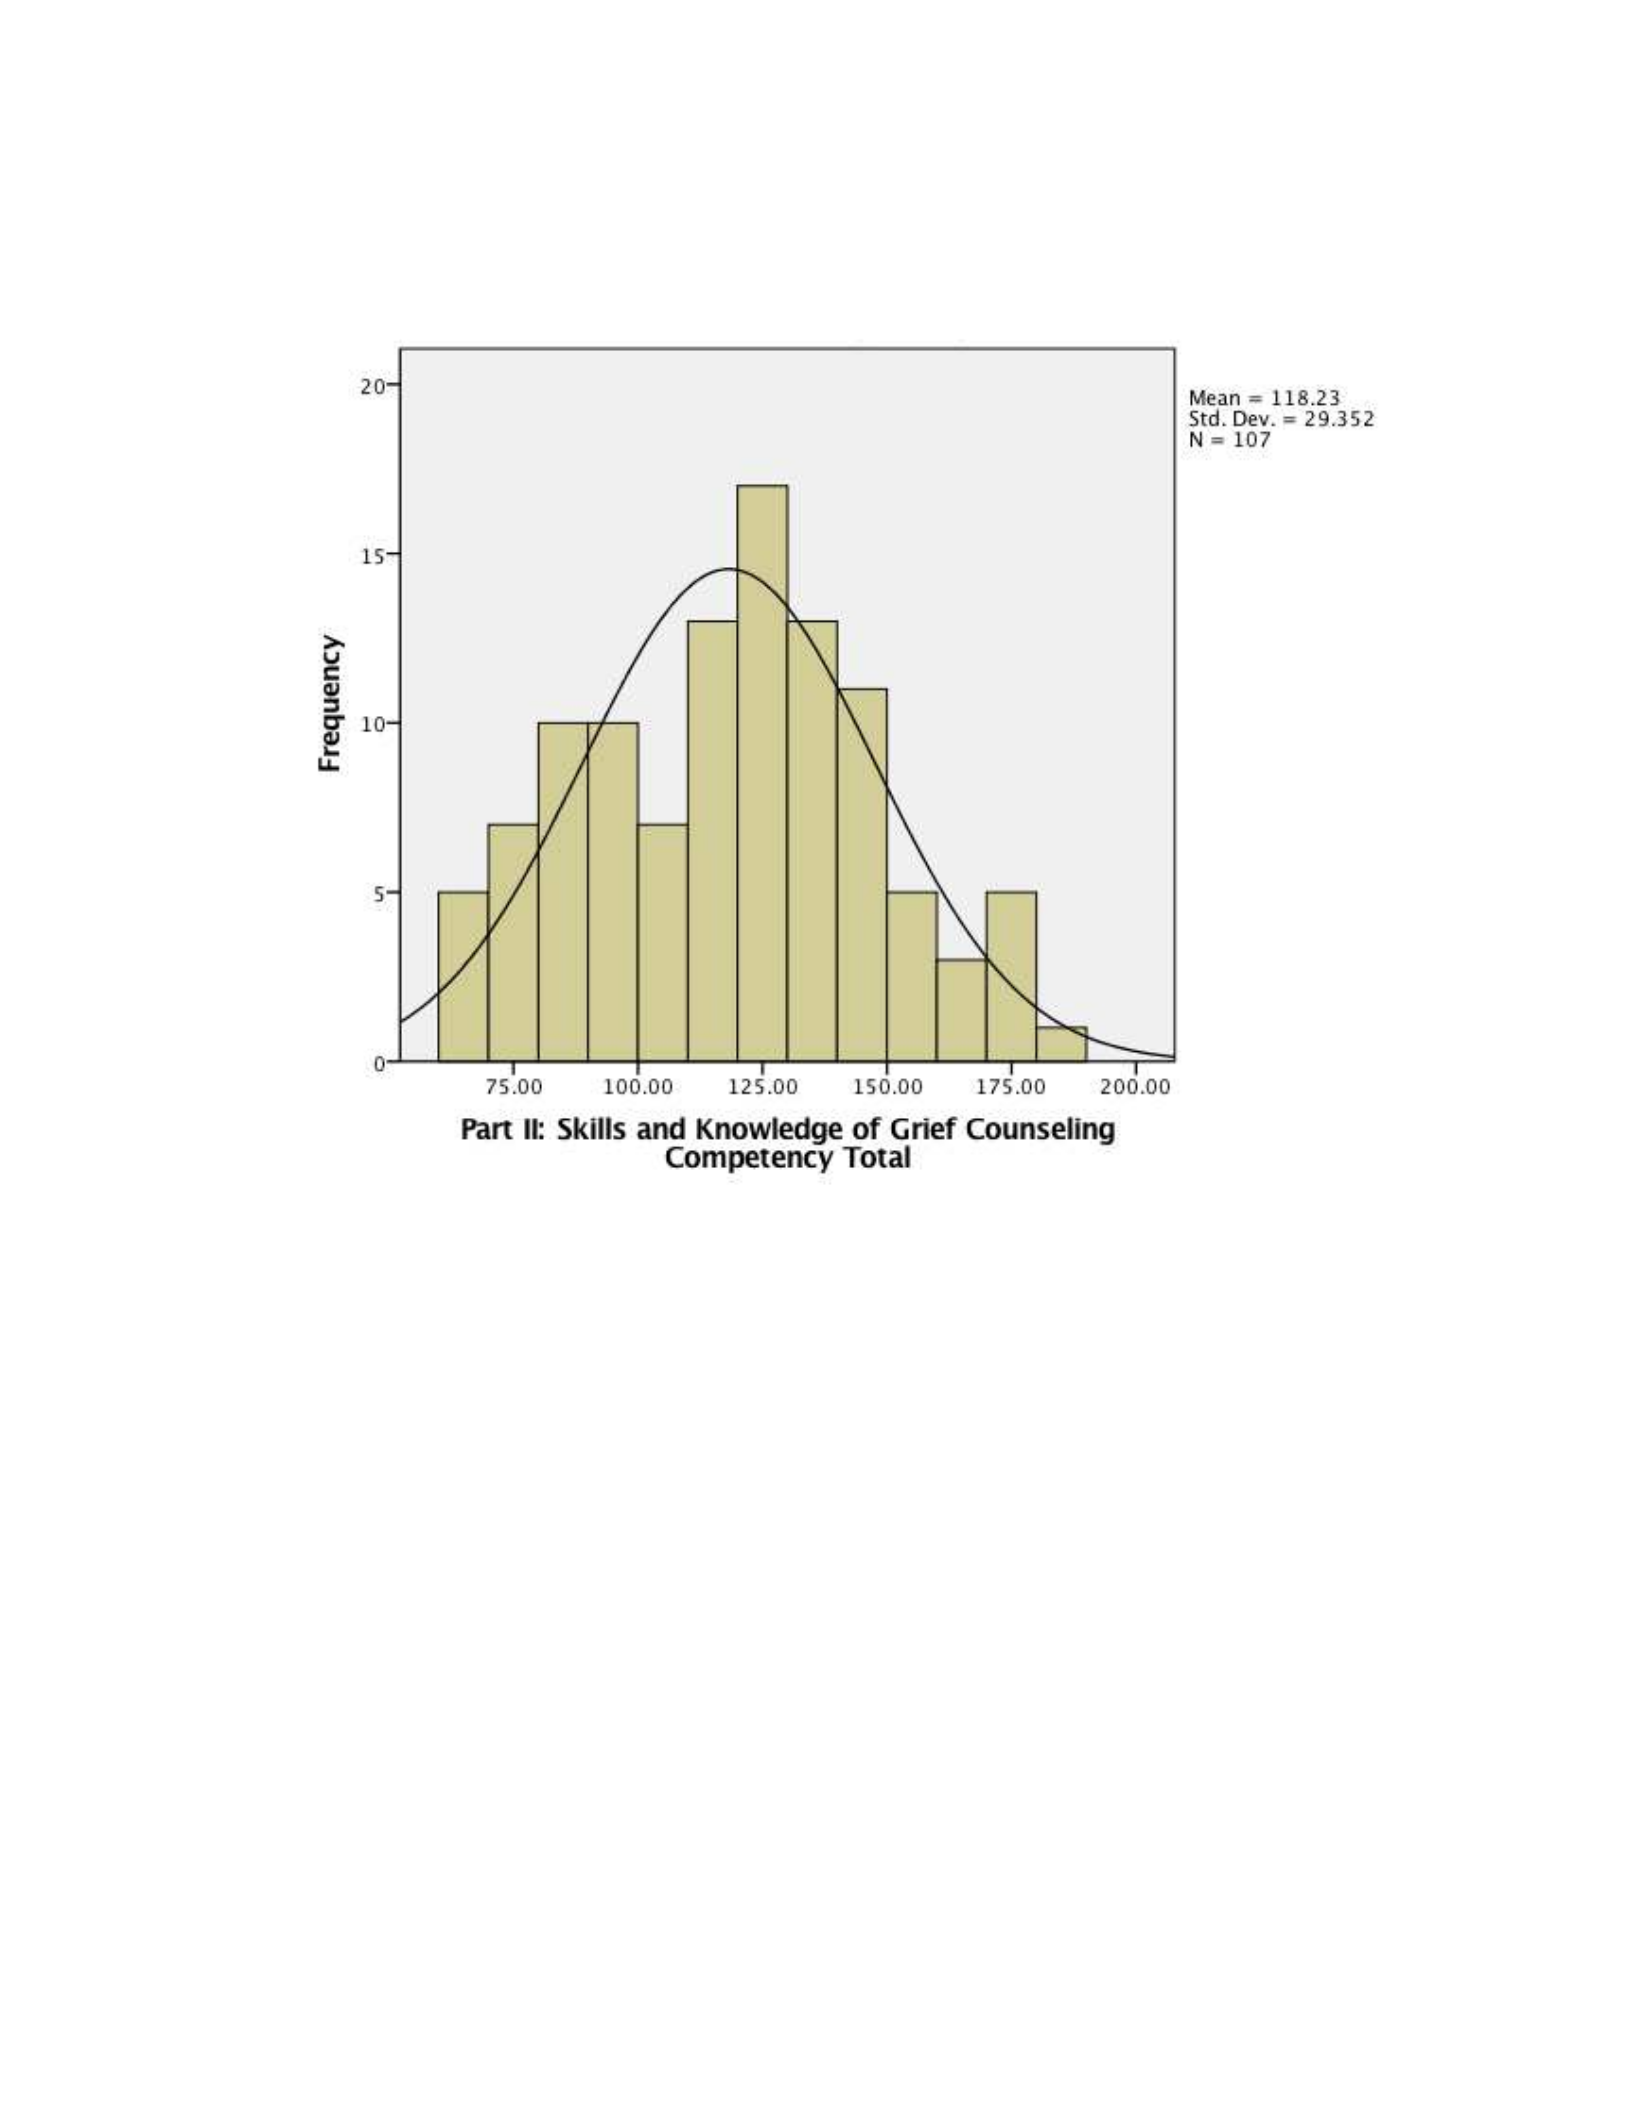
104
Figure 2. Frequency distribution of skills and knowledge of grief counseling competency
105
Table 8
Part
II:
Skills and Knowledge Grief
Counseling Competency Response
Totals
N Valid 107
Missing 46
Mean 118.23
Median 122.00
Mode 129.00
Std. Deviation 29.35
Skewness .049
Kurtosis -.606
Range 122.00
Minimum 60.00
Maximum 182.00
Percentiles
25 94.0
50 122.0
75 139.0
An interquartile range was completed to examine the distribution of 50% of the
scores around median and found scores ranged from 2.5 to 3.8 out of possible 5. This
data shows there was a wide 1.3 range of scores on the skills and knowledge of grief
counseling competencies section of the GCCS while the majority of scores were between
“this barely describes me” and “this somewhat describes me.” Participants’ were
informed in the study information “if there is a question that you choose not to answer,
you may skip the question”. Part 2 of the GCCS in reference to skills and knowledge of

106
grief counseling competencies mean, median, mode, and standard deviation can be found
in Table 9.

107
Table 9
Part II: Skills and Knowledge Grief Counseling Competency
N
Mean Median
Mode
S.D. Valid
Missing
Conceptual Skills and Knowledge
5. I can define and articulate the
nature of "normal" grief and loss as
detailed by theoretical models.
123
30
2.7561
3.00
2.00
1.28255
9. I can describe general
differences in grief and loss as a
function of personality style.
123
30
2.7724
3.00
4.00
1.26629
12. I can articulate a grief
consultation model for parents,
teachers, and other adults about
how to talk to children about grief
and loss.
123
30
2.4065
2.00
1.00
1.27933
14. I can define and articulate the
nature and symptoms of
complicated/unresolved grief
situations.
121
32
2.7603
3.00
3.00
1.21809
25. I can describe common
dysfunctional coping styles of a
person who is grieving loss.
121
32
3.3967
3.00
3.00
a
1.10664
29. I maintain an updated library of
grief and loss resources for clients.
123
30
2.3496
2.00
1.00
1.43140

108
Part II: Skills and Knowledge Grief Counseling Competency
N
Mean Median
Mode
S.D. Valid
Missing
32. I can describe common
functional coping styles of the
person who is grieving.
122
31
3.2787
3.00
4.00
1.17313
34. I can describe how various
individual counseling theories can
be applied to grief counseling with
individuals and families.
122
31
2.8279
3.00
4.00
1.25766
36. I can describe how various
family counseling theories can be
applied to grief counseling with
individuals and/or families.
121
32
2.4628
2.00
1.00
a
1.29770
Assessment Skills
1. I can assess for unresolved loss
and grief that may not be stated as a
presenting problem.
123
30
3.1138
3.00
3.00
.97681
4. I can provide educational
workshops and activities to
community members about loss and
grief.
123
30
2.3008
2.00
1.00
a
1.13755
10. I can conduct suicide
assessments.
122
31
3.9918
4.00
5.00
1.01636
13. I can provide crisis intervention
services to schools and/or
community settings.
123
30
3.0325
3.00
2.00
1.29902

109
Part II: Skills and Knowledge Grief Counseling Competency
N
Mean Median
Mode
S.D. Valid
Missing
16. I can assess a client’s sense of
spirituality.
123
30
3.5528
4.00
4.00
1.01790
18. I can work on an
interdisciplinary team by
interacting with staff from different
professions.
123
30
4.2846
4.00
5.00
.87329
20. I can utilize family assessment
techniques to examine interaction
patterns and roles.
123
30
3.1951
3.00
3.00
1.19190
26. I can assess individuals'
progress on theoretically defined
grief tasks.
121
32
2.7686
3.00
2.00
1.25007
30. I can identify cultural
differences that affect assessment in
relation to loss and grief.
122
31
3.0820
3.00
3.00
1.18942
Treatment Skills
2. I can provide psycho-education
to clients related to the grief
experience for themselves and
others.
123
30
3.2358
3.00
4.00
1.08704
3. I can facilitate family grief
counseling sessions.
123
30
2.3333
2.00
2.00
1.17812

110
Part II: Skills and Knowledge Grief Counseling Competency
N
Mean Median
Mode
S.D. Valid
Missing
6. I can facilitate individual grief
counseling sessions.
123
30
3.1220
3.00
4.00
1.27128
7. I can provide developmentally
appropriate programs about grief
and loss issues in schools.
121
32
2.4298
2.00
2.00
1.30273
8. I can facilitate group grief
counseling sessions.
120
33
2.7667
3.00
3.00
1.25513
11. I can facilitate multi-family
group grief counseling sessions.
123
30
2.0325
2.00
1.00
1.13755
15. I can teach clients how to
obtain support and resources in the
community in relation to grief and
loss.
123
30
3.3821
3.00
3.00
1.21817
17. I can develop rapport with
clients of all ages.
122
31
4.3934
4.00
5.00
.66254
19. I can identify cultural
differences that affect treatment.
123
30
4.0081
4.00
4.00
.78402
21. I can provide appropriate crisis
debriefing sessions.
122
31
3.1475
3.00
3.00
a
1.23095
22. I can exhibit effective active
listening skills.
123
30
4.6667
5.00
5.00
.62288

111
Part II: Skills and Knowledge Grief Counseling Competency
N
Mean Median
Mode
S.D. Valid
Missing
23. I can read and apply current
research and literature related to
grief and effective treatment
interventions.
123
30
3.8455
4.00
4.00
1.00843
24. I can facilitate a reframe of loss
experience and grief reactions for
client empowerment.
123
30
3.4146
4.00
4.00
1.20059
27. I can use the creative arts in
counseling to facilitate grief
expression.
122
31
3.2131
3.00
4.00
1.28069
28. I can appropriately self-
disclose related to my own grief
and loss experiences.
122
31
3.6475
4.00
4.00
1.12023
31. I can recognize and work with
grief related resistance and denial.
122
31
3.0410
3.00
3.00
1.15277
33. I can participate in informal or
formal support groups for
professionals who work with issues
of grief and loss to prevent burnout
and vicarious traumatization.
122
31
3.0000
3.00
3.00
1.27273
35. I can recommend helpful
articles and books for grieving
individuals and families.
122
31
2.7705
3.00
2.00
1.36537

112
Part II: Skills and Knowledge Grief Counseling Competency
N
Mean Median
Mode
S.D. Valid
Missing
37. I can listen in a non-judgmental
way to stories clients tell about their
losses.
122
31
4.6393
5.00
5.00
.59008
a. Multiple modes exist. The smallest value is shown.
The second portion of the survey was furthered studied, by examining the three
sub-sections individually. The first sub-section examined was perceived conceptual skills
and knowledge, which had nine questions. The scores for each question ranged from 1:
“This does not describe me,” to 5: “This describes me very well.” The higher total score,
the higher perceived conceptual skills and knowledge of grief counseling competency.
The total score can range from low of 9 to high of 45.
One hundred and sixteen participants reported in conceptual skills and knowledge
section of the GCCS (M = 25.20, SD = 9.20). The median score for this section was 25
with a mode score of 18, with a frequency of 9, and total scores ranging from a low 9
with a frequency of 2, to high of 45 with frequency of 2 (see Table 10 and Figure 3). The
distribution scores were Kurtosis -.87 and Skewness .23, (see Table 11).

113
Table 10
Conceptual Skills and Knowledge Response Totals
Frequency Percent
Valid
Percent
Cumulative
Percent
Valid 9.00 2
1.3
1.7
1.7
10.00 2
1.3
1.7
3.4
11.00 1
.7
.9
4.3
12.00 4
2.6
3.4
7.8
13.00 2
1.3
1.7
9.5
14.00 4
2.6
3.4
12.9
15.00 6
3.9
5.2
18.1
17.00 3
2.0
2.6
20.7
18.00 9
5.9
7.8
28.4
19.00 7
4.6
6.0
34.5
20.00 4
2.6
3.4
37.9
21.00 3
2.0
2.6
40.5
22.00 3
2.0
2.6
43.1
23.00 3
2.0
2.6
45.7
24.00 3
2.0
2.6
48.3
25.00 5
3.3
4.3
52.6
26.00 5
3.3
4.3
56.9
27.00 3
2.0
2.6
59.5
28.00 7
4.6
6.0
65.5
30.00 4
2.6
3.4
69.0
31.00 3
2.0
2.6
71.6
32.00 2
1.3
1.7
73.3
33.00 4
2.6
3.4
76.7
34.00 5
3.3
4.3
81.0
35.00 2
1.3
1.7
82.8
36.00 6
3.9
5.2
87.9
37.00 2
1.3
1.7
89.7
38.00 4
2.6
3.4
93.1

114
Conceptual Skills and Knowledge Response Totals
Frequency Percent
Valid
Percent
Cumulative
Percent
39.00 1
.7
.9
94.0
41.00 2
1.3
1.7
95.7
42.00 1
.7
.9
96.6
44.00 2
1.3
1.7
98.3
45.00 2
1.3
1.7
100.0
Total 116
75.8
100.0
Missing System 37
24.2
Total 153
100.0
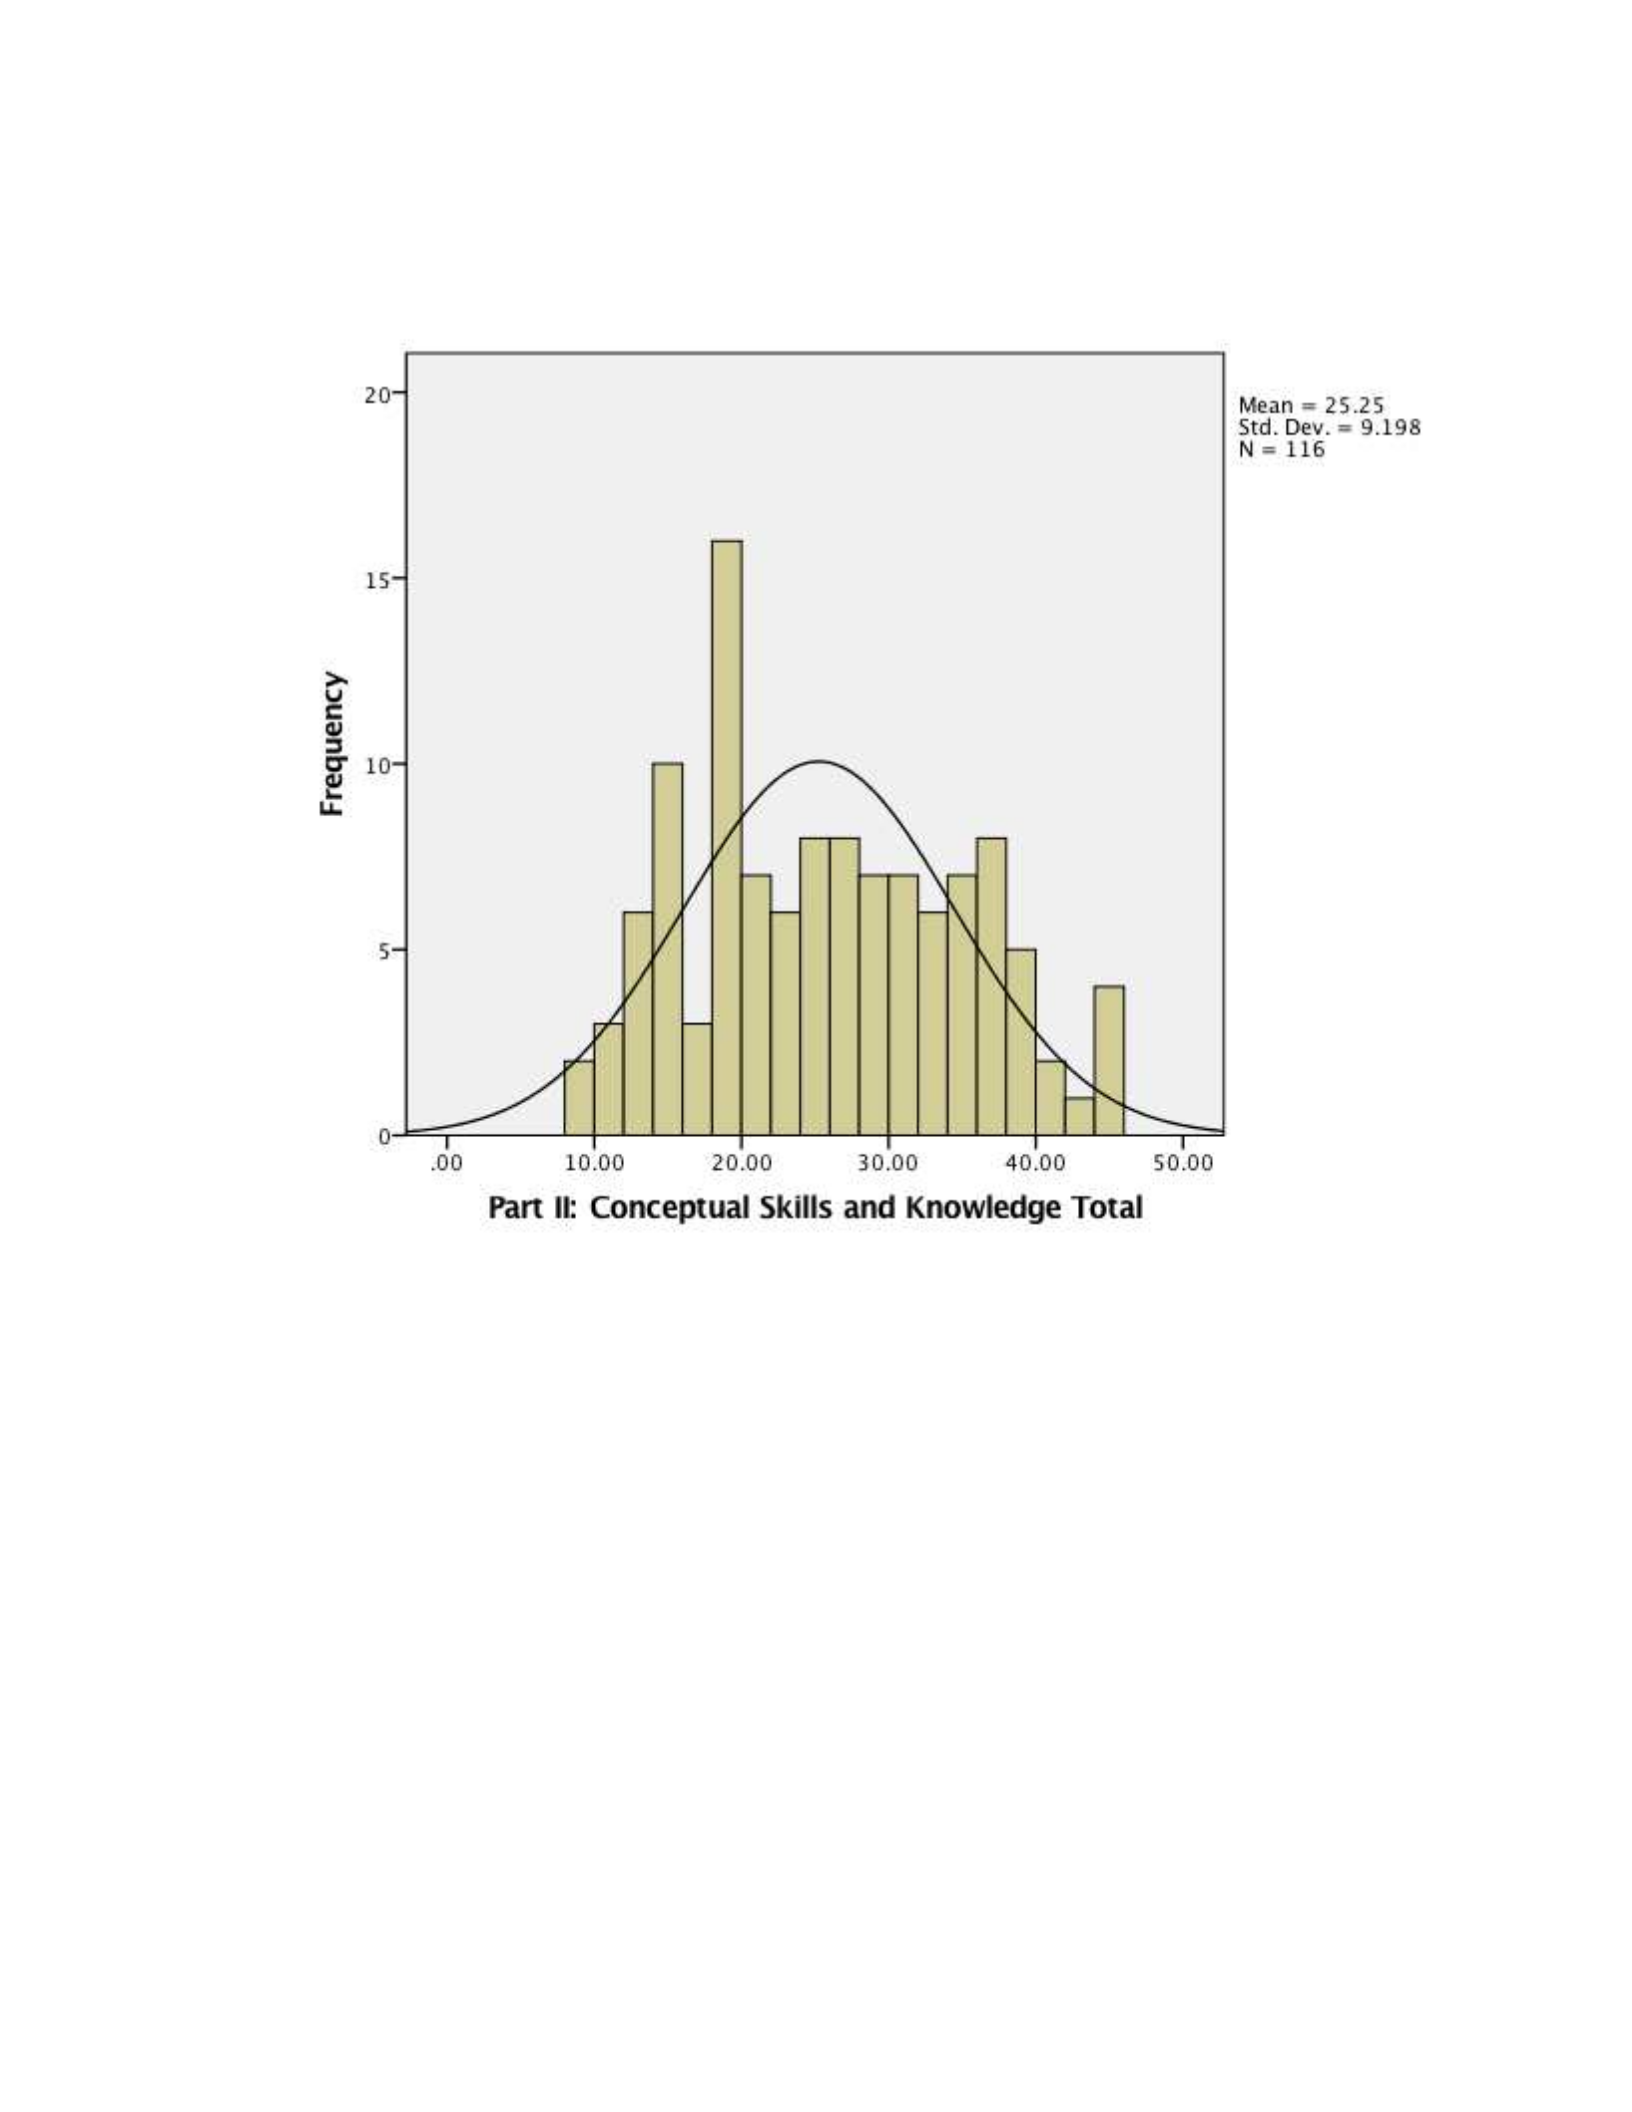
115
Figure 3. Frequency distribution of conceptual skills and knowledge

116
Table 11
Part II: Conceptual Skills and
Knowledge
Response Totals
Statistics
N Valid 116
Missing 37
Mean 25.20
Median 25.00
Mode 18.00
Std. Deviation 9.20
Skewness .23
Kurtosis -.87
Range 36.00
Minimum 9.00
Maximum 45.00
Percentiles
25 18.00
50 25.00
75 33.00
An interquartile range was completed to examine the distribution of 50% of the
scores around median and found scores ranged from 2 to 3.6 out of possible 5. This data
shows there was a wide 1.6 range of scores on the conceptual skills and knowledge sub-
section of the GCCS while the majority of scores were between “this barely describes
me” and “this somewhat describes me.” The conceptual skills and knowledge sub-section
of the GCCS mean, median, mode, and standard deviation can be found in Table 9.
The second sub-section examined was perceived assessment skills, which had
nine questions. The scores for each question ranged from 1: “This does not describe me,”
to 5: “This describes me very well.” The higher total score, the higher perceived

117
assessment skills on the GCCS survey. The total score can range from low of 9 to high of
45.
One hundred and nineteen participants reported in assessment skills section of the
GCCS (M = 29.29, SD = 6.70). The median score for this section was 29 with a mode
score of 34, with a frequency of 10, and total scores ranging from a low 14 with a
frequency of 2, to high of 45 with frequency of 1 (see Table 12 and Figure 4). The
distribution scores were Kurtosis -.426 and Skewness .068, (see Table 13).

118
Table 12
Part II: Assessment Skills Response Totals
Frequency Percent
Valid
Percent
Cumulative
Percent
Valid 14.00 2
1.3
1.7
1.7
17.00 1
.7
.8
2.5
18.00 2
1.3
1.7
4.2
19.00 4
2.6
3.4
7.6
20.00 2
1.3
1.7
9.2
21.00 6
3.9
5.0
14.3
22.00 4
2.6
3.4
17.6
23.00 5
3.3
4.2
21.8
24.00 4
2.6
3.4
25.2
25.00 7
4.6
5.9
31.1
26.00 3
2.0
2.5
33.6
27.00 6
3.9
5.0
38.7
28.00 8
5.2
6.7
45.4
29.00 9
5.9
7.6
52.9
30.00 5
3.3
4.2
57.1
31.00 4
2.6
3.4
60.5
32.00 7
4.6
5.9
66.4
33.00 7
4.6
5.9
72.3
34.00 10
6.5
8.4
80.7
35.00 1
.7
.8
81.5
36.00 7
4.6
5.9
87.4
37.00 2
1.3
1.7
89.1
38.00 2
1.3
1.7
90.8
39.00 2
1.3
1.7
92.4
40.00 2
1.3
1.7
94.1
41.00 1
.7
.8
95.0
42.00 2
1.3
1.7
96.6
43.00 3
2.0
2.5
99.2
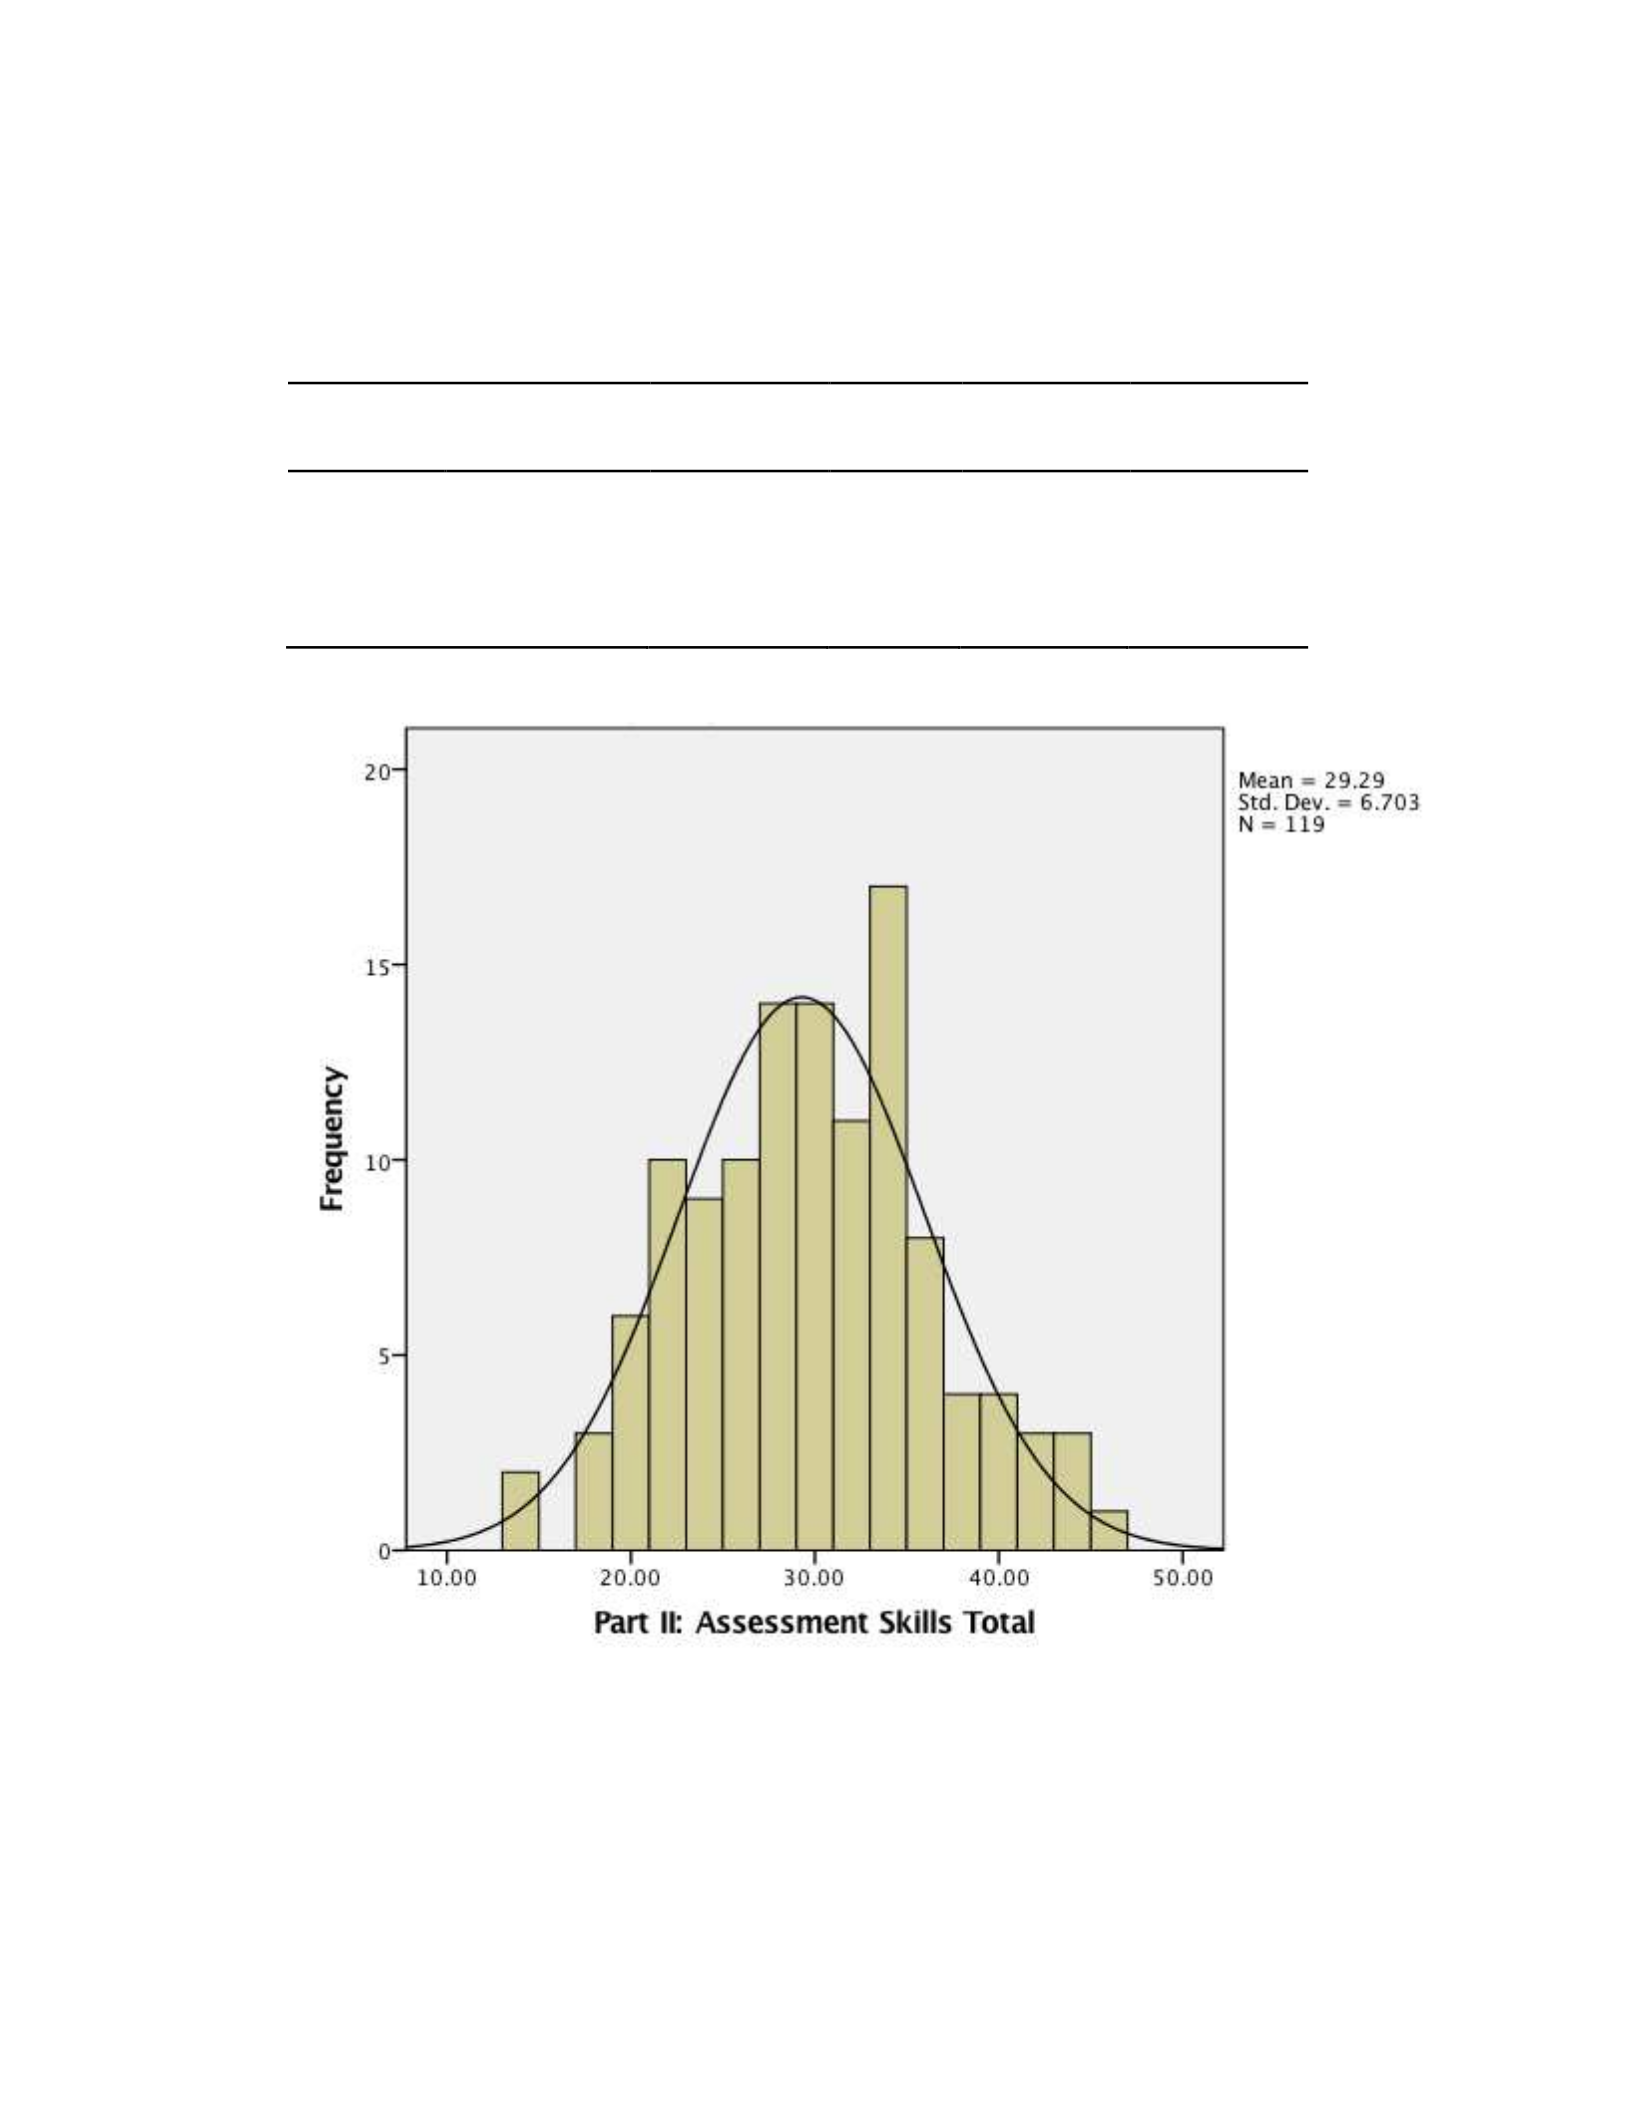
119
Part II: Assessment Skills Response Totals
Frequency Percent
Valid
Percent
Cumulative
Percent
45.00 1
.7
.8
100.0
Total 119
77.8
100.0
Missing System 34
22.2
Total 153
100.0
Figure 4. Frequency distribution of assessment skills
120
Table 13
Part II: Assessment Skills Response Totals
Statistics
N Valid 119
Missing 34
Mean 29.29
Median 29.00
Mode 34.00
Std. Deviation 6.70
Skewness .068
Kurtosis -.426
Range 31.00
Minimum 14.00
Maximum 45.00
Percentiles 25 24.00
50 29.00
75 34.00
An interquartile range was completed to examine the distribution of 50% of the
scores around median and found scores ranged from 2.6 to 3.7 out of possible 5. This
data shows there was a wide 1.3 range of scores on the assessment skills sub-section of
the GCCS while the majority of scores were between “this barely describes me” and “this
somewhat describes me.” The assessment skills sub-section of the GCCS mean, median,
mode, and standard deviation can be found in Table 9.
The last sub-section examined was treatment skills, which had 19 questions. The
scores for each question ranged from 1: “This does not describe me,” to 5: “This

121
describes me very well.” The higher total score, the higher perceived treatment skills on
the GCCS survey. The total score can range from low of 19 to high of 95.
One hundred and thirteen participants reported in treatment skills section of the
GCCS (M = 63.49, SD = 14.35). The median score for this section was 65 with a mode
score of 71, with a frequency of 6, and total scores ranging from a low 33 with a
frequency of 1, to high of 95 with frequency of 1 (see Table 14 and Figure 5). The
distribution scores were Kurtosis -.426 and Skewness .068, (see Table 15).

122
Table 14
Part II: Treatment Skills Response Totals
Frequency
Percent Valid Percent
Cumulative
Percent
Valid 33.00 1
.7
.9
.9
34.00 1
.7
.9
1.8
39.00 2
1.3
1.8
3.5
40.00 2
1.3
1.8
5.3
41.00 1
.7
.9
6.2
42.00 1
.7
.9
7.1
43.00 5
3.3
4.4
11.5
44.00 2
1.3
1.8
13.3
45.00 1
.7
.9
14.2
47.00 4
2.6
3.5
17.7
48.00 2
1.3
1.8
19.5
49.00 2
1.3
1.8
21.2
50.00 1
.7
.9
22.1
51.00 4
2.6
3.5
25.7
52.00 1
.7
.9
26.5
53.00 1
.7
.9
27.4
54.00 2
1.3
1.8
29.2
55.00 3
2.0
2.7
31.9
56.00 1
.7
.9
32.7
57.00 1
.7
.9
33.6
58.00 1
.7
.9
34.5
59.00 3
2.0
2.7
37.2
60.00 2
1.3
1.8
38.9
61.00 3
2.0
2.7
41.6
62.00 2
1.3
1.8
43.4
63.00 3
2.0
2.7
46.0
64.00 4
2.6
3.5
49.6
65.00 3
2.0
2.7
52.2
123
Part II: Treatment Skills Response Totals
Frequency
Percent Valid Percent
Cumulative
Percent
66.00 1
.7
.9
53.1
67.00 5
3.3
4.4
57.5
68.00 2
1.3
1.8
59.3
69.00 3
2.0
2.7
61.9
70.00 1
.7
.9
62.8
71.00 6
3.9
5.3
68.1
72.00 5
3.3
4.4
72.6
73.00 6
3.9
5.3
77.9
74.00 4
2.6
3.5
81.4
76.00 3
2.0
2.7
84.1
77.00 3
2.0
2.7
86.7
79.00 1
.7
.9
87.6
80.00 1
.7
.9
88.5
81.00 1
.7
.9
89.4
83.00 2
1.3
1.8
91.2
84.00 1
.7
.9
92.0
85.00 1
.7
.9
92.9
88.00 3
2.0
2.7
95.6
89.00 1
.7
.9
96.5
90.00 1
.7
.9
97.3
91.00 1
.7
.9
98.2
92.00 1
.7
.9
99.1
95.00 1
.7
.9
100.0
Total 113
73.9
100.0
Missing System 40
26.1
Total 153
100.0
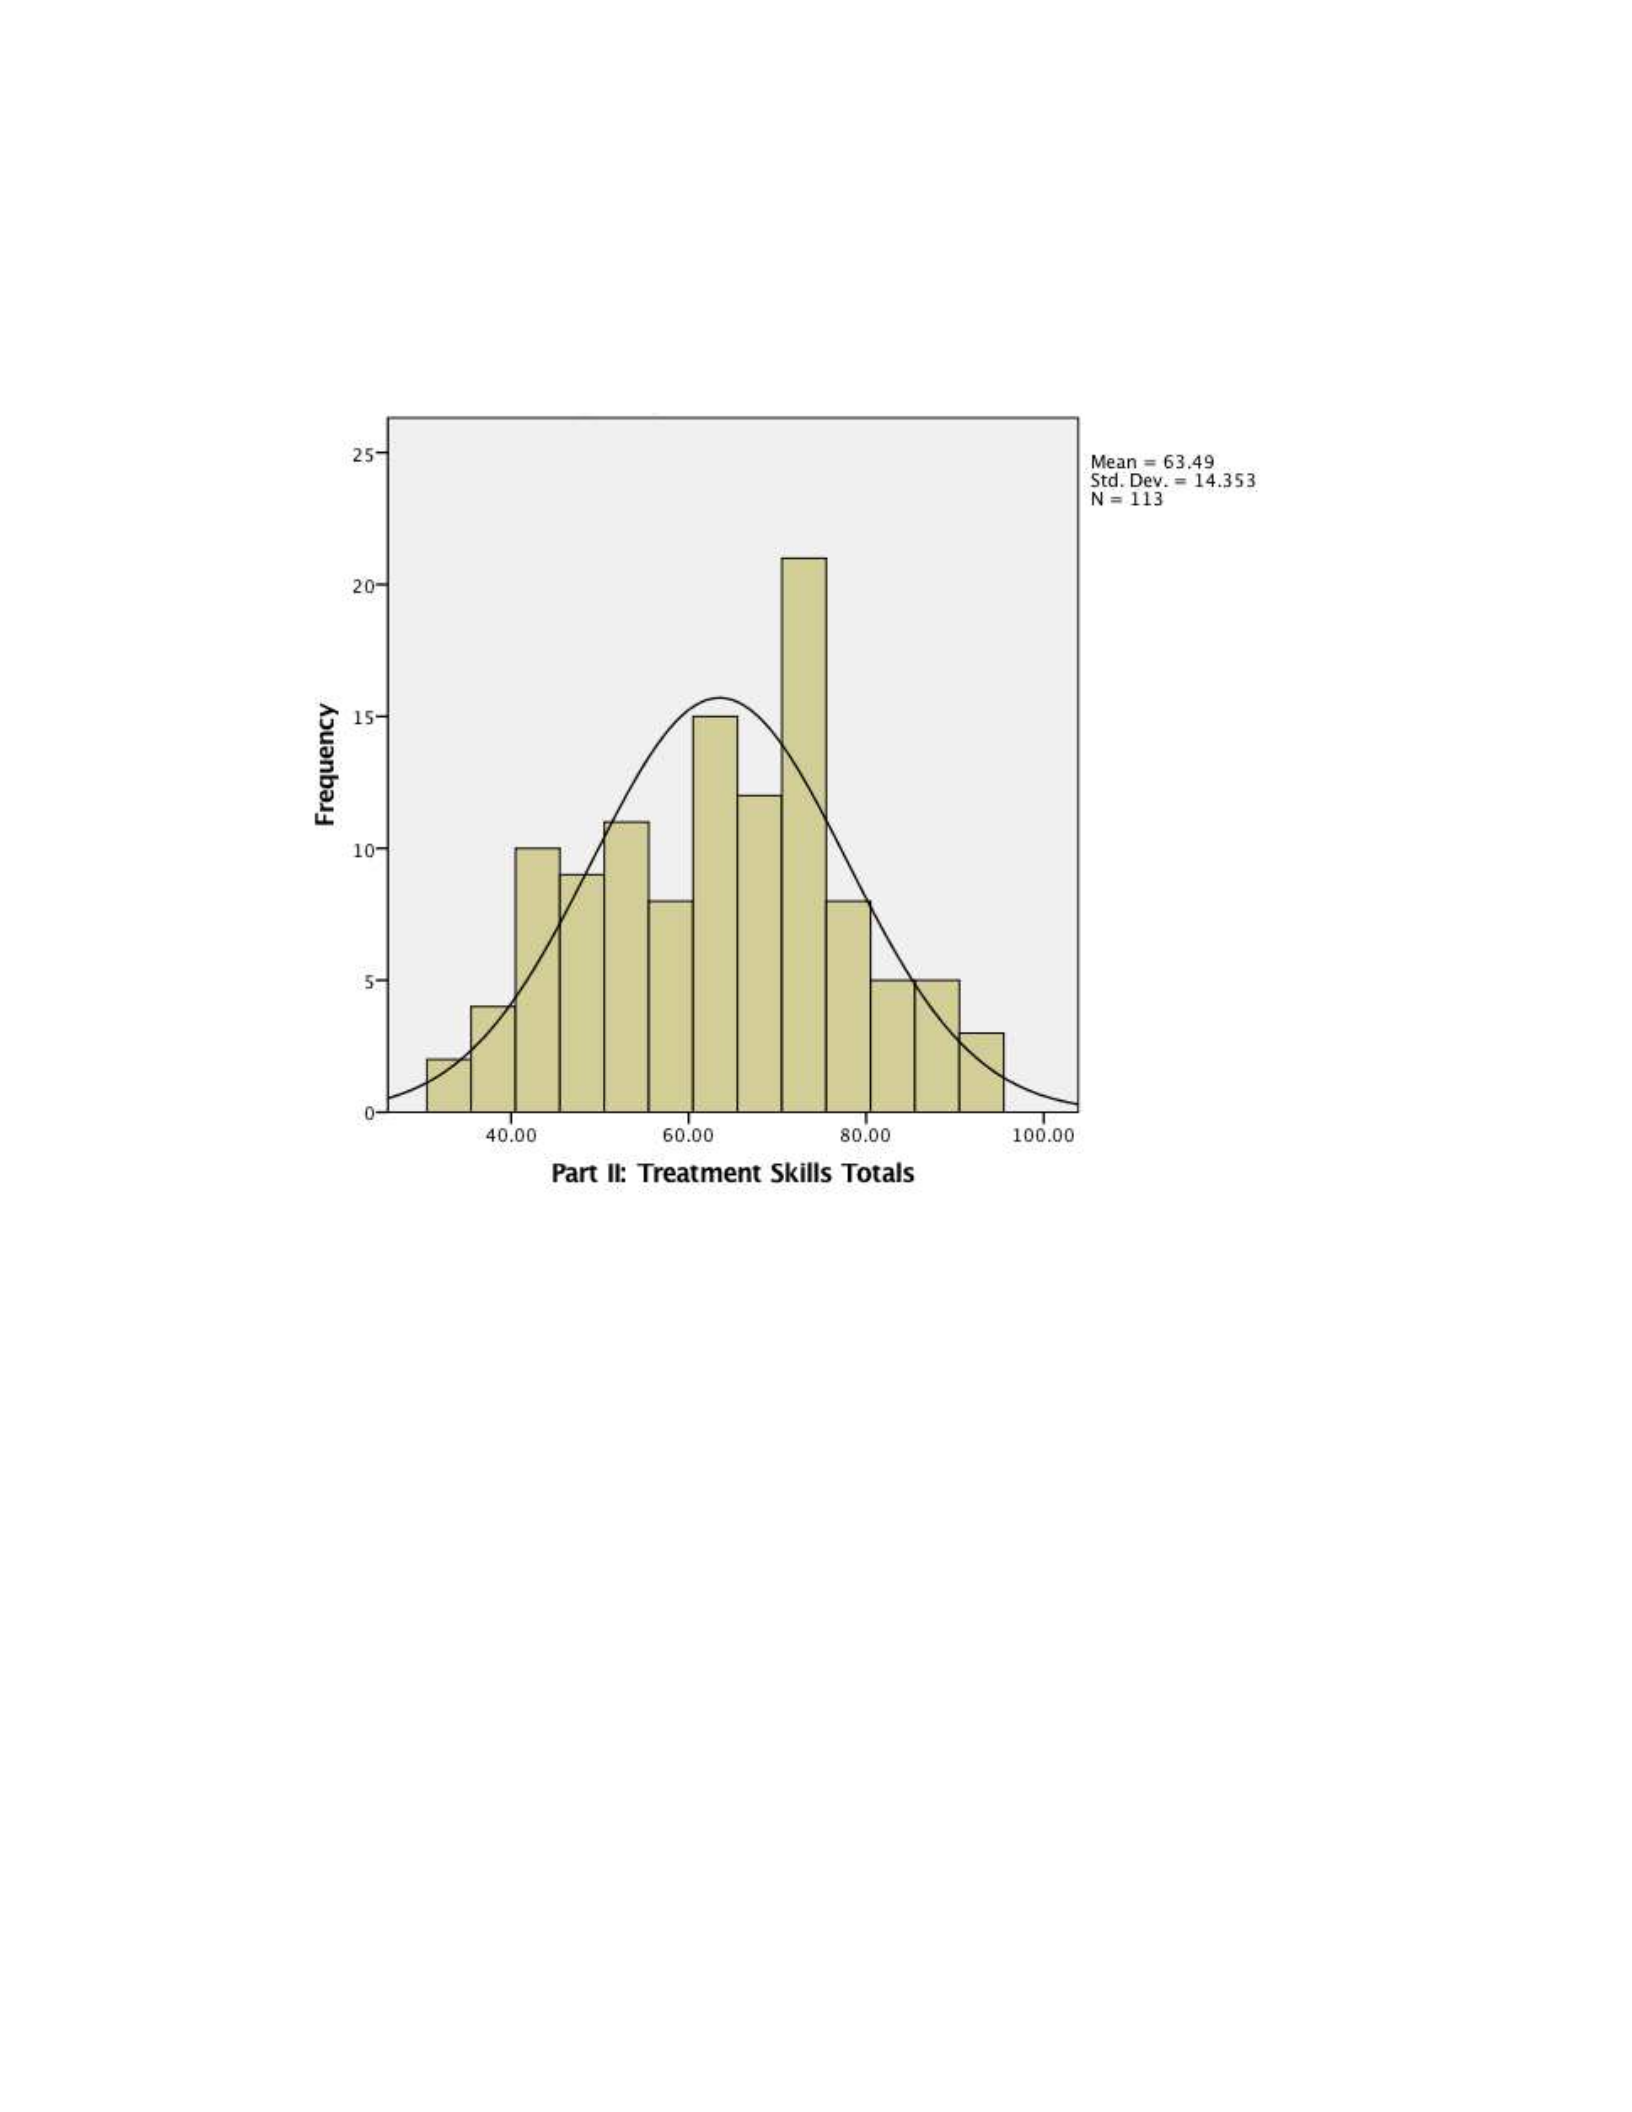
124
Figure 5. Frequency distribution of treatment skills
125
Table 15
Part II: Treatment Skills
Response Totals Statistics
N Valid 113
Missing 40
Mean 63.49
Median 65.00
Mode 71.00
a
Std. Deviation 14.35
Skewness -.037
Kurtosis -.674
Range 62.00
Minimum 33.00
Maximum 95.00
Percentiles 25 51.00
50 65.00
75 73.00
a. Multiple modes exist. The smallest value is shown
An interquartile range was completed to examine the distribution of 50% of the
scores around median and found scores ranged from 2.6 to 3.8 out of possible 5. This
data shows there was a wide 1.2 range of scores on the treatment skills sub-section of
the GCCS while the majority of scores were between “this barely describes me” and “this
somewhat describes me.” The treatment skills sub-section of the GCCS mean, median,
mode, and standard deviation can be found in Table 9.
Findings for Research Question 1
How do the demographic variables (e.g., gender, age bracket, race, and ethnicity)
relate to perceived grief counseling competency?

126
H
o
1: There is no significant (α = .05) interaction effect among the demographic
variables and perceived grief counseling competency.
H
1
1: There is a significant interaction effect among the demographic variables
and perceived grief counseling competency.
This question was investigated using a 4-way MANOVA with demographic
variables (gender, age bracket, race, and ethnicity) as independent variables and the four
grief competency sub scales on the GCCS are the dependent variables.
The first demographic variable gender was examined. Here, 93 females and 12
males were examined for differences on perceived grief counseling competency on the
GCCS survey. No significance for females and males as a function or perceived grief
counseling competency was found (see Table 16).
Table 16
Relationship between Gender and Grief Counseling Competency
Dependent Variable F p η
2
Personal Competency .148
.702
.002
Assessment Skills .531
.468
.007
Treatment Skills .133
.716
.002
Conceptual Skills and Knowledge .280
.598
.003
Next, demographic variable age was compared to the perceived grief counseling
competencies on the GCCS survey for the 105 respondents. A main effect was found for
the presence of age and perceived personal competency related to grief F (16, 236) =

127
2.736, p = .034, indicating that we can reject the hypothesis that there is no significant
interaction effect among the demographics variable age and perceived grief counseling
competency in personal competency. The multivariate η
2
= .12 indicates 12% of
multivariate variance of the dependent variable personal competency is associated with
age (see Table 17).
Table 17
Relationship between Age and Grief Counseling Competency
Dependent Variable F p η
2
Personal Competency 2.736
.034
.120
Assessment Skills .603
.661
.029
Treatment Skills .682
.607
.033
Conceptual Skills and Knowledge .713
.585
.034
One hundred and five participant’s demographic variable race was compared to
the perceived grief counseling competency on the GCCS survey. There was no
significance found for race and perceived grief counseling competency (see Table 18).
Table 18
Relationship between Race and Grief Counseling Competency
Dependent Variable F p η
2
Personal Competency 1.867
.097
.123
Assessment Skills .319
.925
.023
Treatment Skills .666
.678
.048
Conceptual Skills and Knowledge .414
.867
.030

128
One hundred and five participant’s demographic variable ethnicity was compared
to the perceived grief counseling competency on the GCCS survey. There was no
significance found for ethnicity and perceived grief counseling competency (see Table
19).
Table 19
Relationship between Ethnicity and Grief Counseling Competency
Dependent Variable F p η
2
Personal Competency 1.136
.340
.041
Assessment Skills .769
.515
.028
Treatment Skills .042
.988
.002
Conceptual Skills and Knowledge .260
.854
.010
In summary, there was no effect found for demographic variables gender, race,
and ethnicity and perceived grief counseling competency, however, there was
significance found for demographic variable age and perceived grief counseling
competency in regards to personal competency on the GCCS survey. Overall, the
hypothesis was partially supported.
Findings for Research Question 2
Controlling for course offerings (whether the participant’s course curriculum
offered coursework in grief counseling theories and practice), what is the relationship
between coursework and grief counseling competency?
H
o
2: There is no significant (α = .05) positive relationship between coursework
taken and the four grief counseling competency scales, controlling for course offerings.

129
H
1
2: There is a significant positive relationship between coursework taken and the
four grief counseling competency scales, controlling for course offerings.
This question was investigated using a MANCOVA where the independent
variable is coursework; the four grief competency sub scales on the GCCS are the
dependent variables, and the covariate is course offering. This analysis examined the
relationship between course work taken and the four grief competency sub scales on the
GCCS survey.
Controlling for course offerings, a main effect was found having taken course
work in either grief theories or grief interventions, and competency in the grief
counseling competency scales dependent variable assessment Skills, treatment Skills, and
conceptual skills and knowledge (see Table 20). A main effect was found for the
presence of coursework taken and perceived assessment skills related to grief counseling
competency F (12, 254) = 3.134, p = .029, indicating that we can reject the hypothesis
that there is no significant positive relationship between coursework taken and perceived
grief counseling competency in assessment skills, controlling for course offerings. The
multivariate η
2
= .087 indicates 8.7 % of multivariate variance of the dependent variable
assessment skills is associated with coursework taken and grief counseling competency
(see Table 20). A main effect was found for the presence of coursework taken and
perceived treatment skills related to grief counseling competency F (12, 254) = 3.252, p
= .025, indicating that we can reject the hypothesis that there is no significant positive

130
relationship between coursework taken and perceived grief counseling competency in
treatment skills, controlling for course offerings. The multivariate η
2
= .090 indicates
9.0% of multivariate variance of the dependent variable treatment skills is associated with
coursework taken and grief counseling competency (see Table 20). A main effect was
found for the presence of coursework taken and perceived conceptual skills and
knowledge related to grief counseling competency F (12, 254) = 4.986, p = .003,
indicating that we can reject the hypothesis that there is no significant positive
relationship between coursework taken and perceived grief counseling competency in
conceptual skills and knowledge, controlling for course offerings. The multivariate η
2
=
.131 indicates 13.1% of multivariate variance of the dependent variable conceptual skills
and knowledge is associated with coursework taken and grief counseling competency
(see Table 20).
Table 20
Relationship between Course Work Taken and Grief Counseling Competency
Dependent Variable F p η
2
Personal Competency 1.527 .212 .044
Assessment Skills 3.134 .029 .087
Treatment Skills 3.252 .025 .090
Conceptual Skills and Knowledge 4.986 .003 .131
In summary, there was no effect found for coursework taken and perceived grief
counseling competency in relationship to personal competency. However, there was
significance found for a relationship between coursework taken and grief counseling
competency in the dependent variables assessment skills, treatment skills, and conceptual

131
skills and knowledge on the GCCS survey. Overall, the hypothesis was partially
supported.
Findings for Research Question 3
What is the relationship between practicum or internship setting and perceived
grief counseling competency?
H
o
3: There is no significant (α = .05) relationship for clinical setting and
perceived grief counseling competency.
H
1
3: There is a significant relationship for clinical setting and perceived grief
counseling competency.
This question was investigated using a MANOVA whereas the independent
variable is practicum or internship setting and the four grief competency sub scales on the
GCCS are the dependent variables. This examined the relationship between practicum or
internship setting and perceived grief counseling competencies on the GCCS survey.
Of the 107 participants who responded to this section of the GCCS survey, no
significant relationship was found between practicum or internship setting and the
following: perceived personal competency, F (24, 340) = .982, p = .441, η
2
= .056,
perceived assessment skills, F (24, 340) = 1.464, p = .198, η
2
= .081, perceived treatment
skills, F (24, 340) = .751, p = .610, η
2
= .043, or perceived conceptual skills and
knowledge, F (24, 340) = .633, p = .704, η
2
= .037 (see Table 21). Hypothesis was

132
supported; there is no significant relationship for clinical setting and perceived grief
counseling competency.
Table 21
Relationship between Practicum/Internship Setting and Grief Counseling Competency
Dependent Variable F p η
2
Personal Competency
.982
.441 .056
Assessment Skills
1.464
.198 .081
Treatment Skills
.751
.610 .043
Conceptual Skills and Knowledge
.633
.704 .037
Summary
In summary, Research Question 1: How do the demographic variables (e.g.,
gender, age bracket, race, and ethnicity) relate to perceived grief counseling competency?
There was no effect found for demographic variables gender, race, and ethnicity and
perceived grief counseling competency, however, there was significance found for
demographic variable age and perceived grief counseling competency in regards to
personal competency on the GCCS survey. Overall, the hypothesis for research question
1 was partially supported (see Tables 16-19). Research Question 2: Controlling for course
offerings (whether the participant’s course curriculum offered coursework in grief
counseling theories and practice), what is the relationship between coursework and grief
counseling competency? There was no effect found for coursework taken and perceived
grief counseling competency in relationship to personal competency. However, there was
significance found for a relationship between coursework taken and grief counseling

133
competency in the dependent variables assessment skills, treatment skills, and conceptual
skills and knowledge on the GCCS survey. Overall, the hypothesis was partially
supported (see Table 20). Research Question 3: What is the relationship between
practicum or internship setting and perceived grief counseling competency? Hypothesis
was supported; there is no significant relationship for clinical setting and perceived grief
counseling competency (see Table 21).
In Chapter 5, an interpretation of the findings, limitations of the study, and
recommendations for future research to be conducted will be addressed. Furthermore,
implications of positive social change will be presented. Lastly, recommendations for
professional practice will be discussed.

134
Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of this quantitative study was to examine whether CACREP-
accredited master’s-level counseling students in training perceive they have been
adequately trained in identifying clients’ presenting grief issues and in providing grief
counseling to clients in need. These participants were chosen instead of LPCs because I
wanted to examine how master’s-level counseling students assess themselves in regards
to the education or training they received about grief theories or counseling skills related
to issues of grief interventions in their CACREP-accredited formal coursework in
contrast to knowledge possibly obtained post master’s degree in the field.
Perceptions of CACREP-accredited master’s-level counseling students were
examined by using an adapted version of the GCCS (Cicchetti, 2010). Cicchetti noted he
used a modified version of the DCS (Charkow, 2002). According to Cicchetti,
Charkow’s DCS consist of two parts. The first part of Charkow’s DCS inquired about
personal competencies using nine questions. The second part of Charkow’s DCS inquired
about skills and knowledge competencies using 36 questions (Cicchetti, 2010). The two
parts of Charkow’s DCS had four subheadings, as follows: (a) personal competencies, (b)
conceptual skills and knowledge, (c) assessment skills, and (d) treatment skills.
Charkow’s revised version of the DCS, which was renamed GCCS by Cicchetti (2010) is
a 46-item questionnaire survey using a Likert scale to assess the participant’s personal
competencies, conceptual skills and knowledge, assessment skills, and treatment skills in

135
regards to grief intervention and counseling working with clients with presenting issues
related to loss or grief.
Internal consistency reliability for the GCCS was established by calculating a
Cronbach’s alpha for each section and the sub-scales. An alpha level calculated for the
GCCS was calculated for the two sections of the survey which included Part I: Personal
Competency and Part II: Skills and Knowledge Section. The alpha level for the Personal
Competency section was found to be .69 while the alpha level for the Skills and
Knowledge section the alpha was .97. The alphas for the three subscales of the Part II:
Skills and Knowledge scale were the following: for the Conceptual Skills and Knowledge
scale the alpha was .94, for the Assessment Skills scale the alpha was .85, and for the
Treatment Skills scale the alpha was .93. The alphas for the three subscales of the GCCS
suggested relatively high internal consistency. In addition, the alpha for the overall
section Skills and Knowledge was .97. It was deemed acceptable.
Convenience sampling was used for this study to take advantage of the diverse
populations enrolled in CACREP-accredited institutions listed on the CACREP web site.
The participants for this study were recruited from CACREP-accredited master’s-level
counseling programs throughout the United States. After obtaining the CACREP-
accredited master’s-level counseling programs from the CACREP website, I verified they
were current on CACREP accreditations via the website; I contacted the department chair
via email to explain the study and requested that the information of the study and link be

136
sent to all practicum and internship students to participate in the study. The request had
instructions on where to access the study through SurveyMonkey, which is a secure
online survey builder used to collect data.
Using SurveyMonkey, I created the survey and a survey link was emailed to me. I
copied the survey link into the email I sent out to CACREP-accredited master’s-level
counseling program department chairs in the email inviting the students from their
institution to participate. The invite email was forwarded to CACREP master’s-level
counseling students enrolled in practicum or internships informing them about the study
and inviting anonymously them to participate.
When the participants clicked on the SurveyMonkey link, the entry page has
information about the study including overview and background, procedures, voluntary
commitment to participate in the study, benefits and risks of participating in the study,
information on zero compensation, confidentiality, contact information, and statement on
consent (see Appendix F). After the participants have reviewed the implied consent on
the entry page, participants were directed to enter the survey, verified consent, and
completed the DDS (see Appendix C), and the GCCS survey (see Appendix D). There
was no time limit placed on the participants in completing the survey once they started
the survey.
Following the participant’s completion of the DDS and the GCCS survey, the
participant received a debriefing statement form (see Appendix G). The debriefing

137
statement was used to express gratitude for the participant’s participation, shared
information about how to contact the researcher if needed, reiterated the voluntary
participation in the study, reviewed informed consent information, discussed future
requirements for the study, provided counseling services resources, and shared the study
overview.
Interpretation of the Findings
Of the 153 master’s-level CACREP counselor trainees who were in either their
practicum or internship participated in this study, 136 (89.47%) were female, 16
(10.53%) were male, and one participant chose not to respond. On the demographic
questions regarding ethnicity, 142 (92.81%) identified themselves as No, not Hispanic,
Latino, or Spanish origin, 4 (2.61%) identified themselves as Yes, Mexican, Mexican
American, Chicano, 3 (1.96%) identified themselves as Yes, Puerto Rican, and 4 (2.61%)
identified as Yes, another Hispanic, Latino, or Spanish origin, however, 0 identified as
Cuban. On the demographic questions regarding race, 126 (82.89%) identified
themselves as White, 18 (11.84%) participants identified themselves as Black, African
American, or Negro, 3 (1.97%) identified themselves as American Indian or Alaska
Native, 1 (0.66%) identified them self as Filipino, 2 (1.32%) identified themselves as
Other Asian, 1 (0.66%) identified them self as Guamanian or Charnorro, 1 (0.66%)
identified them self as Other Pacific Islander, and one chose not to respond. All 153
participants responded to the age bracket question, 47 (30.72%) responded in the age

138
bracket of 18-24 years old, 69 (45.10%) responded in the age bracket of 25-34 years old,
13 (8.50%) responded in the age bracket of 35-44 years old, 19 (12.42%) responded in
the age bracket of 45-54, and 5 (3.27%) responded in the age bracket of 55 plus years old.
Reporting on their practicum or internship setting, respondents indicated 72 (47.68%)
were at Community Mental Health settings, 51 (33.77%) were at School settings, 2
(1.32%) indicated at Hospital settings, 1(0.66%) at Rehabilitation setting, 4 (2.65%)
indicated at State Agency, 2 (1.32%) at Residential settings, 19 (12.58%) indicated Other
not Specified settings, and 2 (1.32%) of the participants did not respond.
Of the 153 respondents, 153 reported the program they attended was CACREP-
accredited. The list of CACREP-accredited universities was obtained directly from
CACREP via the CACREP website, verified as current accreditation on the CACREP
website, and noted each university’s department program chair. Twenty-two CACREP-
accredited master’s-level counseling programs responded that the e-mail with the survey
link (study) was sent to their practicum or internship students. Since information
pertaining to which school respondents attended was not obtained, there was no way of
knowing how many students from each school or state participated in the study.
Ninety-nine participants (66%) reported the university they attended did not offer
courses in grief theories, 51participants (34%) reported the university they attended did
offer courses in grief theories, and 3 participants did not respond to the question. Ninety-
five participants (62.91%) reported the university they attended did not offer courses in

139
grief interventions, 56 participants (37.09%) reported the university they attended did
offer courses in grief interventions, and 2 participants did not respond to the question.
One hundred and twenty-two participants (80.26%) reported they had not taken any
courses in grief theories, 27 participants (17.76%) reported they had taken one course in
grief theories, 3 participants (1.97%) reported taken two courses in grief theories, and one
participant did not answer the question. One hundred and thirteen participants (76.87%)
reported they did not take any courses in grief interventions, 30 participants (20.41%)
reported they had taken one course in grief interventions, 4 participants (2.72%) reported
they had taken two courses in grief interventions, and 6 participants did not answer the
question. Participant’s characteristics can be found in Table 3.
Demographic variables revealed a wide variability in terms of gender, ethnicity,
and age bracket. In reference to coursework offered, the responses revealed a small
percentage of 34% in which the institutions offered courses in grief theories and 37.09%
offered course in grief interventions. However, 19.73% of the students took coursework
in grief theories and 23.13% of the students took coursework in grief interventions.
The data for the first research question, how do the demographic variables (e.g.,
gender, age bracket, race, and ethnicity) relate to perceived grief counseling competency?
No significance was found for gender, race, or ethnicity as a function of perceived grief
counseling competency. However, significance was found for the presence of age and

140
perceived personal competency related to grief. The results suggested the older age
bracket of participants’ relate to perceived personal competency in grief counseling.
The data for the second research question, when controlling for course offerings
(whether the participant’s course curriculum offered coursework in grief counseling
theories and practice), what is the relationship between coursework and grief counseling
competency? There was no significant relationship found between coursework taken and
perceived grief counseling competency in relationship to personal competency.
Controlling for course offerings, significance was found between having taken course
work in either grief theories or grief interventions, and competency in the grief
counseling competency scales dependent variable assessment skills, treatment skills, and
conceptual skills and knowledge. Significance was found between coursework taken and
perceived assessment skills related to grief counseling competency. Significance was
found for the presence of coursework taken and perceived treatment skills related to grief
counseling competency. Significance was found for the presence of coursework taken
and perceived conceptual skills and knowledge related to grief counseling competency.
These results should be looked at because significance was found between coursework
and grief counseling perceived competency by the participants pertaining to assessment
skills, treatment skills, and conceptual skills and knowledge.
The data for the third research question examined, what is the relationship
between practicum or internship setting and perceived grief counseling competency? No

141
significant relationship was found between practicum or internship setting and the
following: perceived personal competency, perceived assessment skills, perceived
treatment skills, or perceived conceptual skills and knowledge. The results suggested the
participants perceived their practicum or internship site did not give them training in grief
theories or grief interventions.
In summary, demographic variables gender, race, and ethnicity did not show a
significant relationship to participants perceived grief counseling competency, however,
there was significance found for demographic variable age and participants reported
perceived grief counseling competency in regards to personal competency on the GCCS
survey. There was no significance found for coursework taken and perceived grief
counseling competency in relationship to personal competency. However, there was
significance found for a relationship between coursework taken and grief counseling
competency in the dependent variables assessment skills, treatment skills, and conceptual
skills and knowledge on the GCCS survey. Students reported perceived grief counseling
competencies in coursework taken and competency in assessment skills, treatment skills,
and conceptual skills and knowledge. There is no significant relationship for clinical
setting and perceived grief counseling competency. Indicating, the participants perceived
their practicum or internship site did not promote their training in grief theories or grief
interventions.

142
Relationship of Findings to Prior Studies
After an extensive search of the literature, I did not find any previous studies on
CACREP-accredited master’s-level counseling students enrolled in their practicum or
internship reporting that they had been trained to identify or work with clients presenting
with grief related issues. The closest study found is by Cicchetti (2010) on Graduate
Students’ Self Assessment of Competency in Grief Education and Training in Core
Accredited Rehabilitation Counseling Programs. The study by Cicchetti indicated a need
for CORE to offer courses in grief theories and interventions to assist master’s-level
students in effectively helping the population they serve with presenting grief issues.
Another study found in the literature is by Ober et al. (2012), who surveyed LPCs
on grief training, personal and professional experiences with grief, and their self-
assessment of grief counseling competencies. Ober et al. stated the findings noted the
licensed professional counselor participants that obtained education or training in grief
counseling rated themselves more competent in comparison to the licensed professional
counselor participants that did not complete any education or training in grief counseling.
The results from this study reinforce the need for grief education and training in
CACREP-accredited master’s-level counseling programs. The CACREP standards could
expand the core curriculum requirements to include grief education and training by
providing coursework in grief theories and grief interventions. Finally, grief education
and training should not be limited to master’s-level counseling students enrolled in

143
CACREP-accredited programs, but to all counseling students enrolled in counseling
programs.
Limitations of the Study
The limitations of the study were related to research design, sampling method,
convenience sampling, access to the sample population, and generalizability. A limitation
of using quantitative methods for the research study is that one cannot obtain an in-depth
understanding of the participants lived experience (Creswell, 2009). A limitation of
using the non-experimental, one shot survey research design is that the respondents are
limited in their response to those permitted on the GCCS (Creswell, 2009). Frankfort-
Nacmias and Nacmias (2008) stated content validity is determined by the degree to which
the questions on an instrument are representative of what the instrument was designed to
sample. The GCCS was designed to assess master’s-level student’s competency in grief
counseling (Cicchetti, 2010). The questions on the instrument are representative of what
the instrument was designed to sample.
To research the intended population, individuals were asked to provide support to
the research study. These individuals did not have an invested interest in the research;
therefore, many may not have responded nor participated. The participants for this study
were recruited from CACREP-accredited master’s-level counseling programs through
program directors from each institution noted on the CACREP website. Each institution
had their own policies on the dissemination of the email inviting participants to the study.

144
Therefore, it was not guaranteed that all eligible practicum or internship students were
notified of the study by their faculty. Information pertaining to which school’s students
participated was unfortunately not obtained. This limits knowing how many students
from what schools participated. The criteria for inclusion reduced the number of
participants in the study due to it was intended for counselors in training from CACREP-
accredited institutions enrolled in their practicum or internship experience and did not
take into consideration counselors in training from non-CACREP-accredited counseling
programs.
Due to the population studied and the method used, the overall response rate was
low. While this is expected in surveys using emailing methods (Dillman et al., 2009), the
low response rate prevented generalizability of the findings of the study. The
demographic characteristics of the population varied in gender, ethnicity, age, and
programs throughout the United States, however, the sample was not large enough to
apply the findings to all counselor trainees, as gender, age, and ethnicity were not evenly
distributed.
Internal and External Validity Threats
Threats to internal validity would be (a) history, (b) maturation, (c) regression, (d)
mortality, (e) diffusion of treatment, (f) compensatory/resentful demoralization, (g)
compensatory rivalry, (h) testing, and (i) instrumentation (Creswell, 2009). The
participants in this study were asked to complete a one-time survey online with no

145
interaction and no lapse of time between participation, therefore, reducing the internal
validity threats pertaining to (a) history, (b) maturation, (c) mortality, (d) diffusion of
treatment, (e) compensatory/resentful demoralization, (f) compensatory rivalry, and (g)
testing. Furthermore, the participants volunteered anonymously and no information could
be known about the participants which reduces the internal validity threat of regression.
The instruments used for this study are the same instruments used for all participants (no
changes), with the same written instructions provided at the beginning of the study to all,
therefore, reducing the internal validity threat of instrumentation (Creswell, 2009).
The threats to external validity to this study are (a) interaction of selection and
treatment, (b) interaction of setting and treatment, and (c) interaction of history and
treatment (Creswell, 2009). Due to the recruitment criteria of the participants in this
study, generalizability is limited to CACREP-accredited master’s-level counseling
students. Therefore, the findings will not be generalized to the larger population or other
populations. Additionally, future research during different times of counseling student’s
development may be appropriate. Moreover, replication of this study at a later time may
be useful to determine if the results are the same in both studies.
Recommendations for Future Research
There are several ways in which future research could build upon this current
study. One suggestion would be for the administration of the GCCS instrument to larger
and diverse samples to gather additional information in non-CACREP-accredited

146
counseling programs. Further development of instruments may also help researchers to
capture information about grief counseling competencies in a more depth, useful, and
practical manner. Another suggestion for future research is the development of an
assessment instrument in which measures personal experience with grief and its complex
effect on the counselor and their grief counseling competencies. Future research should
be conducted and include the administration of the assessments used in this study to a
variety of mental health professionals such as psychologist, psychiatrist, social workers,
and counselors to compare grief counseling competencies across mental health
disciplines. The information could be valuable in determining if other mental health
disciplines provide better education and training on the topic of grief.
Future research should be conducted and include investigation of content and
quality of grief education and training provided to counselors on grief and loss issues.
This study collected data on master’s students’ self-assessment of competency in grief
education and training in CACREP-accredited counseling programs; however it did not
investigate the specific education and training on grief topics or the perceived benefit of
the training. Grief counseling theories is a topic researchers could investigate and assess
the quality of education and training beyond the stage and task theories.
Qualitative research may provide valuable data on counselors’ in-depth personal
experiences with loss or grief and their understandings of how their experiences may
impact their work with clients. A qualitative research study may provide participants the

147
opportunity to share their lived experiences pertaining to loss or grief. Furthermore, it
would be interesting to investigate how and what counselors learn about loss or grief and
how they translate the knowledge to their professional work with clients with presenting
issues pertaining to loss or grief.
Implications for Social Change
Few studies have been conducted that pertain to the grieving process and
counselor grief competency levels (Ober et al., 2012). The few studies that have been
conducted were primarily focused on hospice professionals’ competency in grief-related
issues (Werth & Crow, 2009). Recent literature has noted the growing need of grief
counseling within the counseling profession (Breen, 2010).
In the counseling profession, competency is an important component and
expectation of practice (ACA, 2014). Therefore, “achieving entry-level competency
means that a counselor in training met the requirements of their program of study and the
standards of the accrediting agency that aligns with the approved curriculum” (CACREP,
2016). Furthermore, it is incumbent upon the accrediting agency to align the curriculum
with current counseling demands and client needs (Cicchetti, 2010). In addition, it is
important to provide the opportunity for master’s-level counseling students to obtain the
proper skills and tools they need to identify and counsel clients with grief-related issues
(Gamino & Ritter, 2012). The results of this study promoted insight and maybe
awareness for social change in master’s-level counseling programs CACREP core

148
curriculum coursework to include education and training in grief theories, skills, and grief
counseling.
For example, multicultural counseling competency was not addressed in
CACREP core courses until counseling demands and client needs became evident in the
counseling profession (Sue & Sue, 2008). Current research has indicated a gap in
literature and that is why I conducted this study to help bridge the gap in literature and
promote positive change in the counseling profession pertaining to grief competency,
education, and training to assist clients with their presenting needs (Ober et al., 2012).
Recommendations for Professional Practice
Recommended curricular inclusion on grief and loss education includes
attachment theory, dual process model of grief, meaning making theory, and adaptive
grieving styles (Doughty Horn, Crews, & Harrawood, 2013; Humphrey, 2009; Reeves,
2011; Waldrop, 2011). Furthermore, adding a social and cultural diversity component on
identifying societal attitudes regarding loss, grief, and explore cultural rituals for grieving
would be helpful (Doughty Horn, Crews, & Harrawood, 2013; Humphrey, 2009; Reeves,
2011; Waldrop, 2011). Adding to the human growth and development section of
curriculum, students may be instructed to create a lifeline of losses, journal about their
losses (written or via video), or have them tell a story about their experiences pertaining
to loss and grief (Doughty Horn, Crews, & Harrawood, 2013; Humphrey, 2009;
Neimeyer & Currier, 2009; Neimeyer, Torres, & Smith, 2011; Parikh, Janson, &

149
Singelton, 2012). Grief and loss can be included in the career development curriculum by
addressing job loss, financial security, loss of identity, self-respect, career changes, and
social status (Doughty Horn, Crews, & Harrawood, 2013; Harris & Isenor, 2011; Sterner,
2012; Walsch, 2009). Grief and loss can be incorporated in crisis counseling courses in
addressing a survivor’s reaction to trauma, loss of limbs, or way of life before the
traumatic event in one’s life (Doughty Horn, Crews, & Harrawood, 2013; Mancini, Prati,
& Bonanno, 2011). In clinical courses such as practicum and internship experiences,
students can look through a lens of loss or grief when a client changes their lifestyle
(Doughty Horn, Crews, & Harrawood, 2013; Doka, 2002). As for group work, existential
group techniques can be taught along with group psychotherapy for grief or curriculum-
based model for grief support groups could be incorporated in CACREP core area
(Doughty Horn, Crews, & Harrawood, 2013; Joyce, Ogrodniczuk, Piper, & Sheptycki,
2010; Rosner, Lumbeck, & Geissner, 2011).
Summary
The purpose of this study was to examine master’s students’ self-assessment of
competency in grief education and training in CACREP-accredited counseling programs.
Results indicated a need for CACREP-accredited counseling programs to re-evaluate the
current core curriculum requirements. There seems to be a need to expand the current
core curriculum requirements to include grief theories and interventions. Results
suggested that there may be a need for colleges and universities counseling programs to

150
offer courses in grief theories and interventions, to educate and train master’s-level
counseling student to effectively assist clients with grief issues. Furthermore, it is
important for CACREP-accredited colleges and universities working with practicum or
internship sites to make sure students will receive grief education and training when
working with clients presenting with grief issues. The study indicated that a high rate of
participants have not taken any courses in grief theories and interventions. Moreover, the
results from this study indicated that a high rate of participant’s CACREP-accredited
institutions did not offer any courses in grief theories or grief interventions. Ober et al.
(2012) stated licensed professional counselor participants that obtained grief education or
training rated themselves more competent in comparison to the licensed professional
counselor participants that did not complete any grief education or training. This
indicates the need of re-evaluation of CACREP requirements to include grief education
and training in core curriculum.

151
References
Adams, S. A. (2006). Does CACREP accreditation make a difference? A look at NCE
results and answers. Journal of Professional Counseling: Practice, Theory &
Research, 34(1/2), 60–76. Retrieved from
http://web.b.ebscohost.com.ezp.waldenulibrary.org/
Ahmed, S., Wilson, K. B., Henriksen Jr., R. C., & Jones, J. W. (2011). What does it mean
to be culturally-competent counselor? Journal for Social Action in Counseling
and Psychology, 3(1), 17-28. Retrieved from http://www.psysr.org/jsacp/ahmed-
v3n1-11_17-28.pdf
Aladag, M., Yaka, B., & Koc, İ. (2014). Opinions of counselor candidates regarding
counseling skills training. Educational Sciences: Theory & Practice, 14, 879-886.
doi: 10.12738/estp.2014.3.1958
American Counseling Association. (2006). Medicare coverage of licensed
professional counselors. Retrieved from http://www.counseling.org/
American Counseling Association. (2007). Congress passes bill to include
counselors in VA programs [Press release]. Retrieved from
http://www.counseling.org/PressRoom/PressReleases.aspx?AGuid=17fc785a-
1c40-46a3-93fc-06a5df8e4e65
American Counseling Association (2014). ACA Code of Ethics. Alexandria, VA: Author.

152
American Mental Health Counseling Association (2010). AMHCA Code of Ethics.
Alexandria, VA: Author.
Archer, J. (2001). Broad and narrow perspectives in grief theory: Comment on Bonanno
and Kaltman (1999). Psychological Bulletin, 127(4), 554-560. doi:
10.1037//0033-2909.127.4.554
Barstow, S., & Terrazas, A. (2012, March). Medicare needs to cover counselors.
Counseling Today, 54(9), p.11. Retrieved from
http://www.counseling.org/resources/library/Counseling%20Today/March2012C
TOnline.pdf
Bernard, J. M., & Goodyear, R. K. (2009). Fundamentals of clinical supervision (4th
ed.). Upper Saddle River, NJ: Pearson Education.
Bobby, C. L. (2013). The evolution of specialties in the CACREP Standards: CACREP's
role in unifying the profession. Journal of Counseling & Development, 91(1), 35-
43. Retrieved from http://dx.doi.org.ezp.waldenulibrary.org/10.1002/j.1556-
6676.2013.00068.x
Bowlby, J. (1958). The nature of the child’s tie to his mother. International Journal of
Psychoanalysis, 39, 350-371. Retrieved from
http://www.psychology.sunysb.edu/attachment/online/nature%20of%20the%20ch
ilds%20tie%20bowlby.pdf
Bowlby, J. (1980). Attachment and loss (Vol. 3). New York, NY: Basic Books.

153
Breen, L. J. (2010). Professionals' experiences of grief counseling: Implications for
bridging the gap between research and practice. Omega: Journal of Death &
Dying, 62, 285-303. doi: 10.2190/OM.62.3.e
Breen, L. J., & O’Conner, M. (2011). Family and social networks after bereavement:
Experiences of support, change and isolation. Journal of Family Therapy, 33(1),
98-120. doi: 10.1111/j.1467-6427.2010.00495.x
Brookfield, S. D. (1986). Understanding and facilitating adult learning. San Francisco:
Jossey-Bass.
Carr, E., & Cortina, M. (2011). Heinz Kohut and John Bowlby: The men and their ideas.
Psychoanalytic Inquiry, 31(1), 42-57. doi: 10.1080/07351690.2010.512847
Charkow, W. B. (2002). Family-based death and grief-related counseling: Examining the
personal and professional factors that impact counselor competence. (Doctoral
dissertation). Dissertation Abstracts International, 62(12-A), 4070. Retrieved
http://search.proquest.com.ezp.waldenulibrary.org/pqdtglobal/docview/30471064
9/F795C98B6ED4F0DPQ/1?accountid=14872
Chidarikire, S. (2012). Spirituality: The neglected dimension of holistic mental health
care. Advances in Mental Health, 10, 298-302. Retrieved from
http://dx.doi.org.ezp.waldenulibrary.org/10.5172/jamh.2012.10.3.298

154
Cicchetti, R., J. (2010). Graduate students’ self-assessment of competency in grief
education and training in core accredited rehabilitative counseling programs
(Doctoral dissertation). Obtained electronically from the author.
Collier, R. (2011). Grief therapy for those left behind. CMAJ: Canadian Medical
Association Journal, 183, E265-E266. doi:10.1503/cmaj.109-3793
Cordaro, M. (2012). Pet loss and disenfranchised grief: Implications for mental health
counseling practice. Journal of Mental Health Counseling, 34, 283-294. Retrieved
from http://web.b.ebscohost.com.ezp.waldenulibrary.org/ehost/pdfviewer/
Corey, M.A., & Corey, G. (2007). Becoming a helper (5th ed.). Belmont, CA: Thomson
Brooks/Cole.
Council for Accreditation of Counseling and Related Educational Programs. (2016).
CACREP standards. Retrieved from www.cacrep.org
Creswell, J. (2009). Research design: Qualitative, quantitative, and mixed methods
approaches (3rd ed.). Thousand Oaks, CA: Sage Publications.
Currier, J. M., Neimeyer, R. A., & Berman, J. S. (2008). The effectiveness of
psychotherapeutic interventions for bereaved persons: A comprehensive
quantitative review. Psychological Bulletin, 134, 648–661. doi:10.1037/0033-
2909.134.5.648

155
D'Amore, S., & Scarciotta, L. (2011). Los(t)s in transitions: How diverse families are
grieving and struggling to achieve a new identity. Journal of Family
Psychotherapy, 22(1), 46-55. doi:10.1080/08975353.2011.551099
Dillman, D. A., Smyth, J. D., & Christian, L. M. (2009). Internet, mail, and mixed-mode
surveys: The tailored design method. Hoboken, NJ: John Wiley.
Doka, K. J. (Ed.) (2002). Disenfranchised grief. Champaign, IL: Research Press.
Doughty Horn, E. A., Crews, J. A., & Harrawood, L. K. (2013). Grief and loss education:
Recommendations for curricular inclusion. Counselor Education &
Supervision, 52(1), 70-80. doi:10.1002/j.1556-6978.2013.00029.x
Doran, G., & Downing Hansen, N. (2006). Constructions of Mexican American family
grief after the death of a child: An exploratory study. Cultural Diversity & Ethnic
Minority Psychology, 12, 199-211. Retrieved from
http://dx.doi.org.ezp.waldenulibrary.org/10.1037/1099-9809.12.2.199
Duba, J. D., & Magenta, M. (2008). End-of-life decision making: A preliminary outline
for preparing counselors to work with terminally ill individuals. The Family
Journal: Counseling and Therapy for Couples and Families, 16, 384-390.
Retrieved from
http://dx.doi.org.ezp.waldenulibrary.org/10.1177/1066480708323083
Eckerd, L. M. (2009). Death and dying course offerings in psychology: A survey of nine
Midwestern states. Death Studies, 33, 762-770. doi: 10.1080/07481180902961211

