


Research Design on relationship between burnout and emotional intelligence
The research adopted a survey design (Gravetter & Forzaro, 2013). This involved face-to-face
contact with observance of social distancing health recommendations due to the COVID-19
pandemic and also encouraged through the group social media chat. A descriptive quantitative
approach was most appropriate in this context because it allowed the researcher to gather attitudes
and perceptions of the respondents over a short period, hence quick and more financially feasible.
The respondents were engaged in December 2020 to January 2021 where correlational
investigation on burnout and emotional intelligence compiled into one questionnaire was done. The
advantage of this strategy was that it provided data from more than one variable simultaneously.
The levels of burnout and emotional intelligence, and the relationship between these variables for
the healthcare workers in emergency departments at KNH during the study period were analyzed.
Based on this, the relationship between burnout and emotional intelligence was identified. It did
not determine the cause-effect. Likewise, demographic data was surveyed. However, this design is
time bound and does not guarantee representation.
Population
This study was carried out in Kenyatta National Hospital (KNH), a modern center of excellence
and the largest medical facility in the East African region that has been in existence since 1902
then known as King George VI Hospital. KNH has a bed capacity of 1,800 with 26 busy outpatient
clinics (KNH website), and hosting the University of Nairobi and the Kenya Medical Training
College. It is a training center for local and international students, interns, and postgraduate
learners from various institutions. Figure 3 shows the organizational structure.
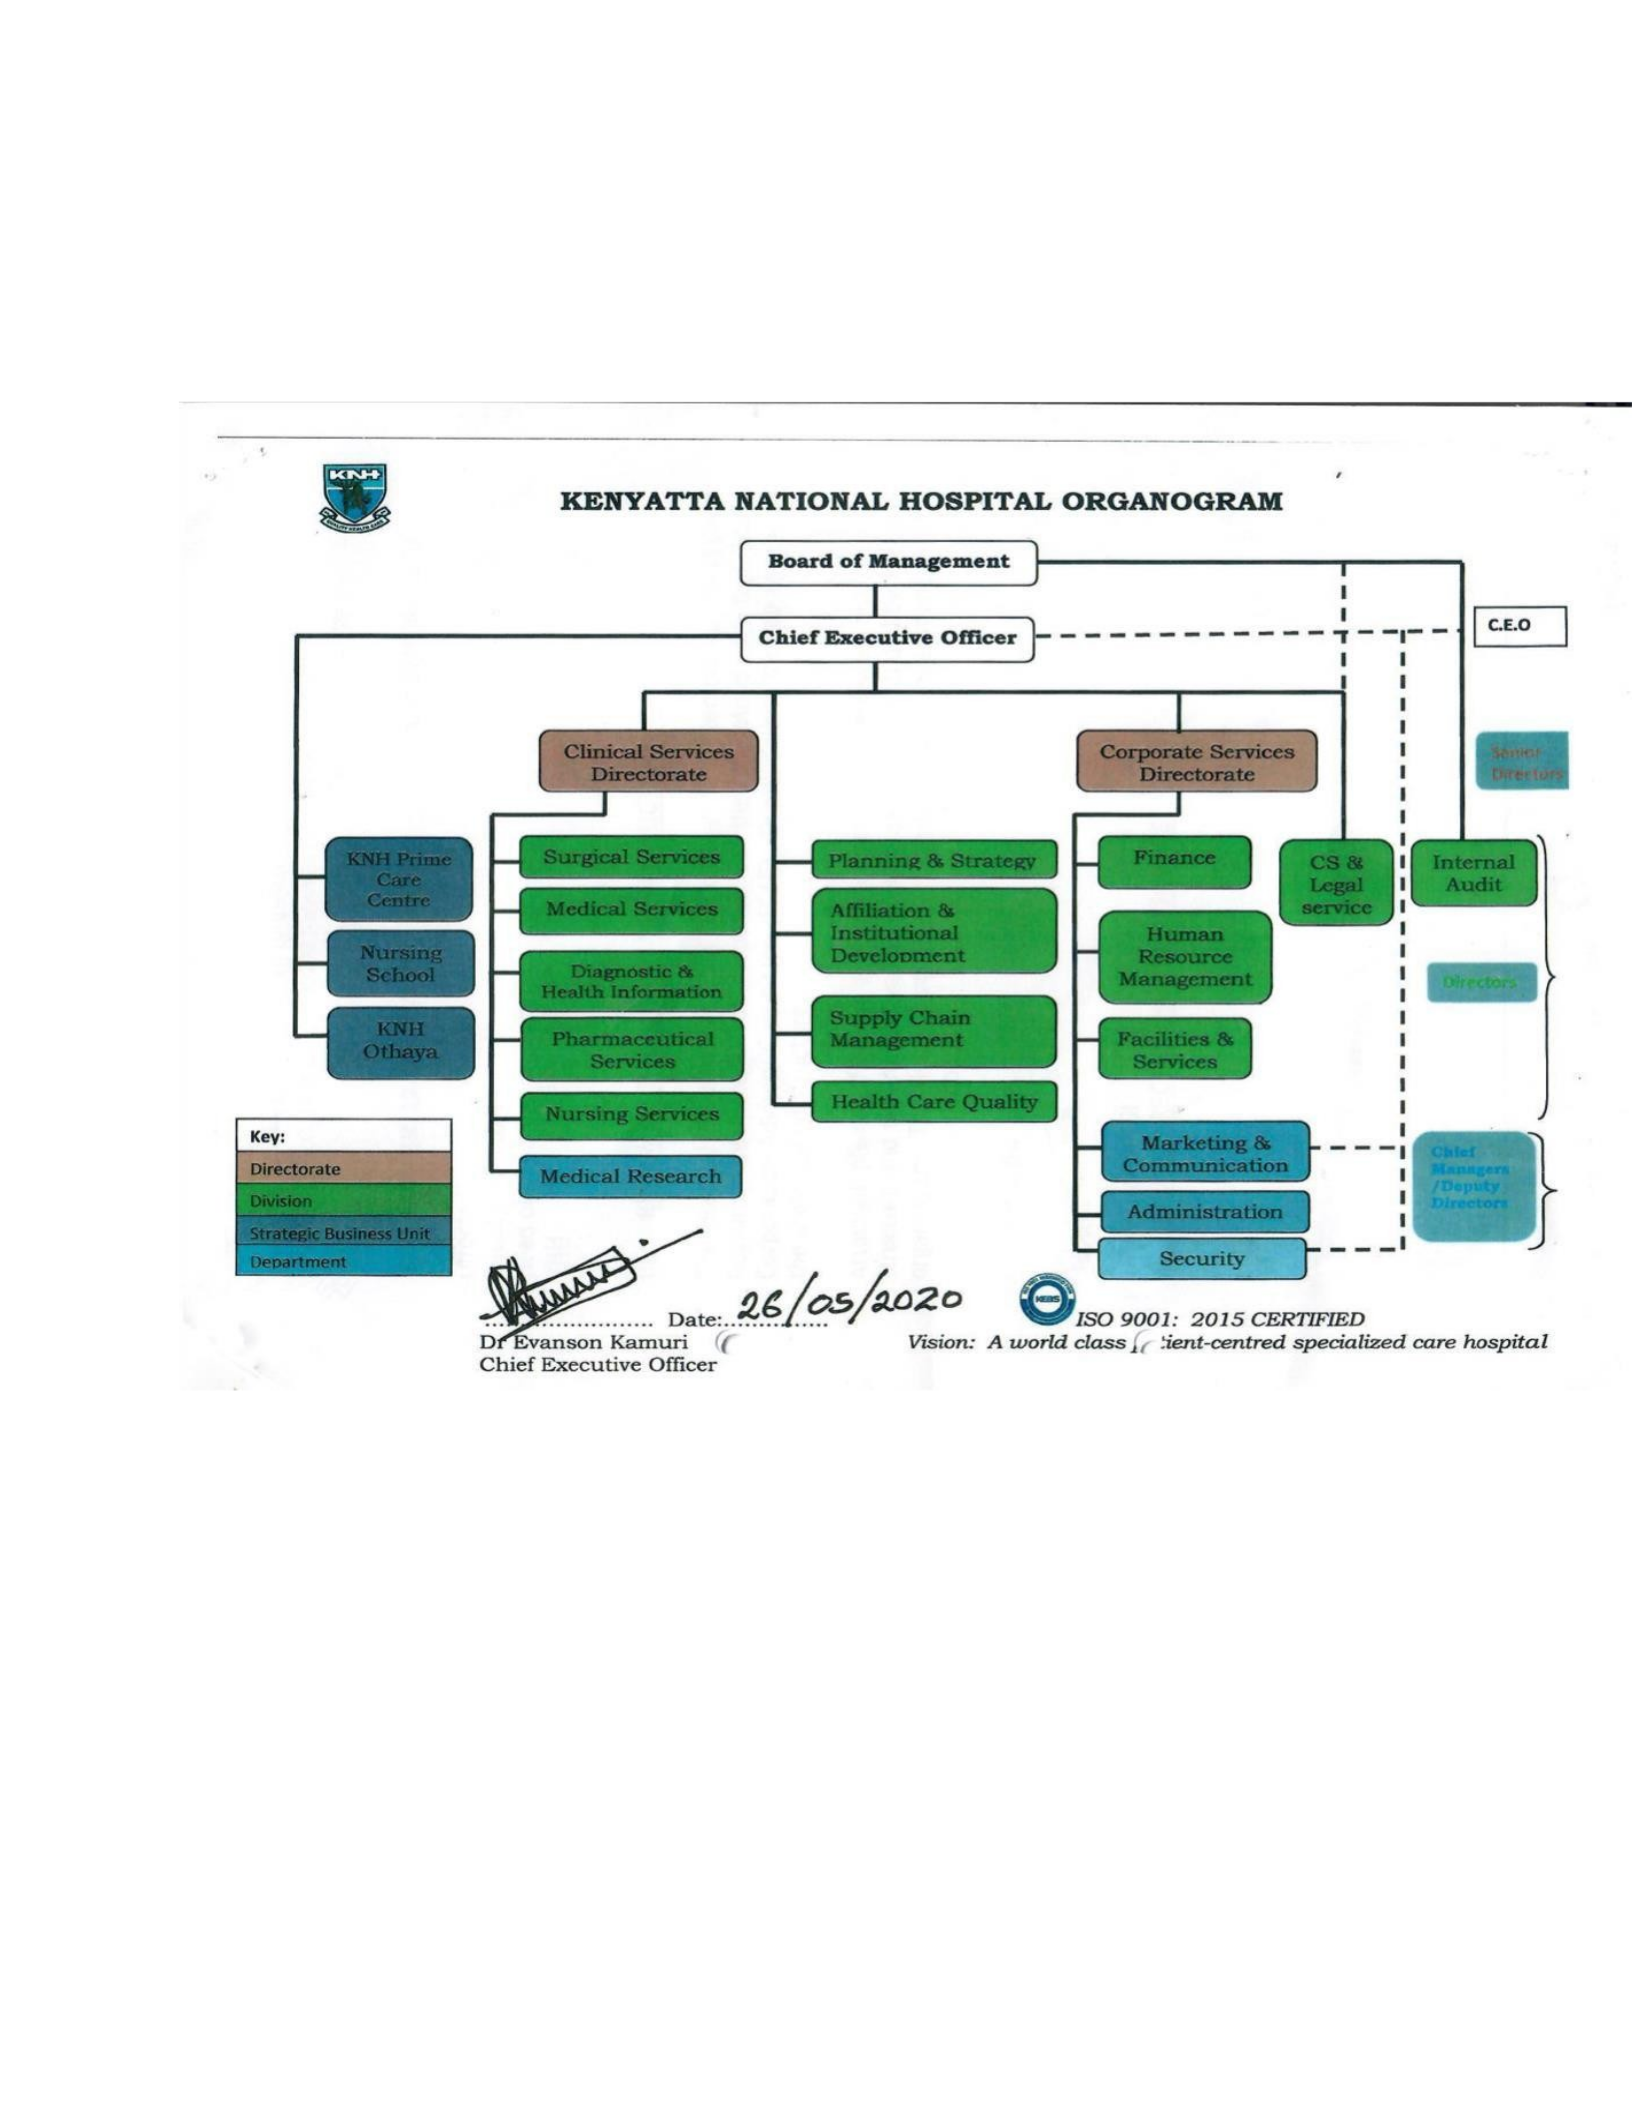
Figure 3 KNH Organizational Structure
Note. Adopted from the Planning and Strategy Department as draft (2020)
31

The general staff population at KNH is 4,800 staff. KNH is a parastatal and a Teaching and
Research Referral hospital (level 6) situated in the Upper Hill area, approximately 4 kilometers via
Haile Selassie Avenue according to Google maps. Figure 3 Shows the organizational structure of
KNH. The clinical services directorate comprises of the following categories: pharmaceuticals,
surgical, medical, nursing, medical research, and diagnostics & Health information departments.
The healthcare workers identified as the study population are drawn from these main departments
and deployed in the emergency departments. According to the Human Resource Department
records there are a total of 300 workers of various job categories in the emergency departments.
These departments are the Accident & Emergency Department and the Pediatric Emergency Unit
that had 218 healthcare workers.
Table 1 outlines a cross tabulation of the job category, the total number of respondents and the
percentage of the HCW in the emergency departments in KNH.
Table 1 Number of Healthcare Workers in Emergency Departments in KNH
Job Category/Title N Percentage
Doctors 46 21%
Nurses 141 65%
Pharmacists 9 4%
Medical Social Workers 6 3%
Clinical officers 16 7%
Total N=218 100%
Note. Statistics from the Human Resource Department, KNH (2020). N = 218
The inclusion criterion was healthcare workers deployed in the emergency departments of the
following professionals: doctors, nurses, clinical officers, medical social workers and
pharmacists. 32

Exclusion criteria included healthcare workers that were away from the institution, those on
preceptor training, probation period and those who had worked in the emergency departments for
less than 6 months. The other KNH workers, any other healthcare workers in ED, and students on
attachment were excluded.
Sampling Design
Sampling Frame
This study targeted only healthcare workers in the following job description: doctors, nurses,
pharmacists, clinical officers, and medical social workers. These are clinical staff working in the
target site, the emergency departments of the hospital. This data was obtained through a telephone
call to the office of the Director, Human Resources Management, KNH.
Sampling Technique
A complete enumeration of the HCW in the emergency departments was selected for this study.
Therefore, convenience sampling technique was used to engage those were willing and available to
participate in the study. The HCW on duty during the study period and met the inclusion criteria
were enrolled.
Sample Size
The study involved the healthcare workers who have worked for over 6 months in the two
emergency departments at KNH. These are the pediatric emergency unit and the accident and
emergency departments. The study used census method for respondent’s determination. This
involved complete enumeration where all the healthcare workers in the target population were
included in the study. The study employed complete enumeration method where all the healthcare
workers in the ED were targeted.

However, in determining the minimum number required for the threshold of the study, Taro
Yamane’s formula for sample size calculation was used. The minimum sample size targeted taking
into consideration the study eligibility criteria was calculated as follows:
n = 1+ ( )^2
where
n is the sample size
N is the total target population (N = 218)
e is the margin of error (e = 10%)
1 is a standard coefficient
The calculation is as follows;
n =
218
1+218(0.1)^2
n = 218
1+2.12
n = 218
3.12
n = 69.871
n = 70
Taking into consideration a 10% non-response which is 7
Thus, the corrected minimum sample size was 70 +7
The minimum sample size targeted was 77.
The total population distribution of the staff is as shown on Table 2. It outlines the number of
HCW by profession working in the accident and emergency department and those working in the
pediatric emergency unit.

Table 2
Population Distribution of Healthcare Workers in Emergency Departments
Job Category/ Title Number of healthcare workers
Accident & Pediatric Emergency Total
Emergency Unit
Doctors 46 0 46
Nurses 116 25 131
Clinical officers 0 16 16
Pharmacists 6 3 9
Medical Social Workers 6 0 9
Total 174 44 n = 218
Data Collection Methods
Sources of Data
A self-administered questionnaire was the main source of primary data. The tool was availed
mainly through WhatsApp social media platform. Secondary data on HCW on duty was gathered
from the office of the Director, Human Resources Management. Additional secondary information
was gathered from books and journals. Occupational and Safety Policies, Mental Health Act,
among others documents were scrutinized.
Self-Administered Questionnaire on Burnout and Emotional Intelligence
A three (3) sections questionnaire compiled on Google forms was administered. The first section
was demographic data and background information that included single item NIDA Quick Screen
for Alcohol/ Tobacco/ Substance Use-Abuse inventory. The other two sections, Part B and Part C
were the Maslach Burnout Inventory and Emotional Intelligence Self-Assessment
tool respectively. 35

The study questionnaire was issued to the respondents as an online link whose responses will be
submitted online. They were required to read and provide consent available in Appendix I, before
completing the self-administered questionnaire available on Appendix II. Attention was drawn to
the briefing and debriefing form on Appendix III. The structured, self-administered 22-item Likert-
scale Maslach Burnout Inventory tool was be used to determine levels of burnout (Maslach,
Jackson & Leiter, 1996).
This tool, Part B of the questionnaire, provided the scoring of the emotional exhaustion [7 items],
depersonalization [7 items], and personal achievement [8 items]. The tool is a 7-point Likert-scale is
rated as follows: ‘0 = Never, 1 = A few times a year, 2 = Once a month, 3 = A few times a month, 4
= once a week, 5 = a few times per week, and 6 = everyday”. In each facet of the self-administered
Maslach Burnout Inventory tool, the scores were summated. For the depersonalization section, a
score of 5 or less indicated low level of burnout, 6 to 11 indicated moderate burnout, while 12 and
over was high level of burnout. For the section on Personal achievement, a score of 33 or less
showed high levels of burnout, between 34 and 39 was moderate levels while scores greater than
40 was low levels of burnout. In total, a score 17 or less indicated low levels of burnout, while 18
and 29 moderate levels, and over 30 high levels indicated of burnout.
The emotional intelligence self-assessment tool in Part C of the self-administered questionnaire
was adapted to collect data on emotional intelligence, it outlined the scoring and was not
copyrighted (Sterrett, 2000). Further, reference to the Emotional Competence Inventory technical
manual that has similar components was made to get additional clarification. This tool is a 20-item
inventory that has Likert-scale ratings ranging from “1= Never to 5= Always”, specifically 1=
never, 2 = rarely, 3= Sometimes, 4= usually and 5 = always. The tool measures
four aspects of emotional intelligence namely: the self-awareness, self-management, social
awareness and relationship management.

The scoring of the instrument includes of having a total of each aspect which could range from 5 to
a high score of 25. Scores below 18 in each area indicate a need to intentionally improve one’s
emotional intelligence while a score 18 and above in each aspect is considered high emotional
intelligence.
Research Procedures
Ethical approval was sought from National Commission for Science Technology and Innovation
(NACOSTI) through the USIU’s Institutional Review Board (IRB) for authorization to carry out
the study. Commendation and consent to conduct study within the institution was sought by
submitting approval request letter (Appendix IV) to the Kenyatta National Hospital – University of
Nairobi, Ethics and Research Committee (KNH-UoN ERC). Upon receipt of approval (Appendix
IX), the researcher informed the heads of the departments of the study and requested for their
logistical support. Sensitization sessions were conducted to orient and brief the staff.
The questionnaire on Google forms link (https://forms.gle/Xbs9u1FYynyhCsvY7), containing the
study consent and instructions to the respondents, was administered by the researcher. Support was
received from team leaders who encouraged staff to complete the questionnaire. The data was
compiled and analyzed in various relevant data management methods.
Pilot Study
A pilot study as indicated on Appendix VI, was conducted in December 2020. The objective was to
allow the researcher to get familiarized with the protocol and conduct a trial on the questionnaire.
This pre-testing was carried out randomly among doctors and nurses in the medical section of the
hospital. The pilot study exposed the researcher to the study process and therefore familiarized to
the distribution, and process of data collection instruments. It informed the researcher of any
anomalies and potential challenges that were anticipated during the study (Thabane et al.,
2010). 37

The length of questionnaire was noted to be a challenge. During the data collection therefore, the
researcher assisted the respondents that had challenges with the online process and encouraged all
to ensure the questionnaire was completed in one sitting.
Reliability of the Instruments
In a study on the single-item NIDA quick screen tool, it was established that the tool had
sensitivity of 73.3 % and specificity of 84.7 % for detecting unhealthy alcohol use. It had
sensitivity of 71.3 % and specificity of 94.3 % for detecting unhealthy drug use and hence adopted
in this study (McNeely et al., 2019; Saitz, Cheng, Allensworth-Davies, Winter, & Smith, 2014).
The reliability coefficients of the MBI tool in sub-Saharan Africa, Nigeria had Cronbach’s Alpha
results of .86, and Split-half of .57 with Odd-Even result of .92 (Coker & Omoluabi, 2009). A
Malawian study identified the reliability of the MBI. They found Cronbach's alpha coefficients for
emotional exhaustion, depersonalization and personal accomplishment to be 0.90, 0.79 and 0.71
respectively. The test-retest reliability range of these was between 0.50 to 0.82 (Thorsen, Tharp, &
Meguid, 2011). The reliability was found ranging 0.83 to 0.92 with alpha Cronbach of the
emotional intelligence tool that has the dimensions of self-awareness, self-management, social-
awareness, and social-relationship. Similarly, a co-efficient range of 0.81 to 0.95 on split-half test
was noted (Sulaiman & Noor, 2015). The tools were therefore used because these reliability results
had delivered consistent results in previous studies.
Validity of the Instruments
The validity test for the burnout tool conducted in Romania had the estimated internal consistency
had Cronbach alpha coefficient of .83 and .84 on frequency and intensity respectively (Năstasă &
Fărcaş, 2015).

The convergent and discriminant validity of this study had Cronbach's alpha coefficients scores of
0.67, 0.42, and 0.60 for emotional exhaustion, depersonalization and personal accomplishment
respectively in a study carried out in Malawi (Thorsen et al., 2011). The validity of the emotional
intelligence tools have been controversial (Miners, Côté, & Lievens, 2017). The validity of
emotional intelligence tool similar in content as the one used in this study was found to have good
criterion validity (Sulaiman & Noor, 2015).
Different tools have been used in Africa to assess emotional intelligence. In their study among
mental health practitioners in Uganda, Kabunga, Anyolitho, and Betty (2020) used the 72-item
tool. It has the self-awareness, self-management, and social awareness components that are similar
to the Emotional Intelligence Tool. The fourth facet is identified as social skills, which the later
describes as social relationship.
This has been standardized comprehensively by Hay Group (2005). The Hay Group (2005)
found .78 and .63 on the average overall internal consistency on aspects of personal and social
emotional intelligence. The pilot study was used to fulfill part of the validity assessment. It was
anticipated, with the validity scores therefore that tools measured what they claimed to measure.
Administration of the Instrument
In December 2020, the department administrators were informed of the data collection tool and
process. Pre-test was carried out in December 2020 and dissemination of the study questionnaire
was carried out in December 2020 to January 2021.
The heads of the emergency departments were informed of the approvals and request made for a
slot to make a presentation to the staff. The study focus was presented to the HCW via virtual
(zoom) meeting on Thursday December 10, 2020. The HCW will be informed about process of the
online administration of the instrument, (https://forms.gle/Xbs9u1FYynyhCsvY7) and concerns
were addressed.
39

Due to the COVID-19 pandemic, the researcher ensured to observe the infection control protocols.
Donning face mask appropriately, use of sanitizer and recommended physical distance was
maintained. The researcher approached the respondents and outlined the purpose of the research.
The link was forwarded the link to respondents and responded to any concerns. Those who
preferred completing at a later time were reminded to complete the link that the researcher
forwarded directly to them through WhatsApp account or they could access it on the common
departmental WhatsApp social media platform. The questionnaire (Appendix II), comprising of the
social demographics that included NIDA quick screen for screen for alcohol/ tobacco and
substance use, the Maslach Burnout Inventory, and emotional intelligence tool was used. It took
the respondents an average of 20minutes to complete the questionnaire.
The strategy used was to disseminate the questionnaire (Appendix II) based on timings of less
workload at the ED. Dissemination of the tool was conducted on weekdays between 7.45am and
8.30am, and 12.45pm and 1.30pm. The sets of timings were selected based shift reporting and
handing over procedures time for the morning section as staff had few patients to attend to. These
timings also provided an opportunity for the researcher to administer the questionnaire to those
who were signing off from duty.
Data Analysis Methods
The data was coded using excel version 10, and exported to Statistical package for social science
(SPSS) version 25 for statistical analysis with assistance from a statistician. A descriptive analysis
of the mean, standard deviation and frequency illustrated the demographic data. Graphical
representations were used to provide analysis of the collected data. These included bar charts,
graphs, tables and pie charts. The data was analyzed descriptively using frequencies and
percentages distributions for the demographics, levels of burnout and emotional intelligence.

The correlation analysis was done using the Pearson product-moment correlation coefficient. The
results were computed from the data analyzed and Pearson correlation coefficient (r) used to
identify the relationship between the dimensions of burnout with each of the two components of
emotional intelligence, and the confounding factors (age, gender, and alcohol and substance use).
Ethical Considerations
Verification and adherence to ethical consideration of the research proposal was presented to the
NACOSTI after the USIU’s institutional review board (IRB) authorization to carry out the study.
Subsequently, the KNH-UoN ethics and research committee (ERC) was contacted via letter for
permission to conduct the study within the hospital (Appendix IV). Evidence of the approval letter
(Appendix IX) from KNH-UoN ERC was submitted to Head of the emergency department before
the study was initiated in the ED.
Confidentiality, Anonymity and Informed Consent
The HCW working in the emergency departments were encouraged to voluntarily complete the
questionnaire and without coercion. Further, to assure confidentiality the respondents were not
required to log in to access the Google forms link and submitted their responses anonymously as
the Google form link not have an identifier linked to the submitted form.
The consent form, Appendix I was attached to the questionnaire that was administered via a Google
forms link. This allowed the respondents to read the consent document (Appendix I) in order to make a
voluntary and informed consent to participate. Completion and submission of the questionnaire was
also considered as informed consent. The consent form provided information to the respondents of their
right to withdraw from the study at any time before submission of the questionnaire.
41

Briefing and Debriefing of the respondents
The staff were briefed, content of respondent briefing and debriefing form (Appendix III) was
shared and clarifications made. To minimize the possibility of deception, the researcher outlined
the study objectives and assured the staff of integrity during the study. A disclosure of “no
competing interest” was declared.

