


1
Chapter 1: Introduction to the Study
Medical school has been identified as a “high stress” field for students (Ayala et
al., 2018). Research has consistently recorded that medical students have regularly
identified stress as a factor that affects their learning and well-being (Al Raddadi et al.,
2017; Anandhalakshmi et al., 2016; Dyrbye et al., 2017; Saravanan & Wilks, 2014).
Stress, as a general term according to the Merriam-Webster dictionary (n.d.), is defined
as “a constraining force or influence, such as: a physical, chemical or emotional factor
that causes bodily or mental tension and may be a factor in disease causation.” Further,
stress is said to be an external constraint, resulting from an interaction between someone
and their surroundings that is recognized as threatening, challenging, or even harmful,
affecting a person mentally and physically (Bhagat et al., 2018). In essence, stress seems
to occur because of pressure combined with a lack of resources to cope with its effect
(Dhandapani et al., 2022).
Rigorous medical school curricula, along with other variables related to medical
training, have been identified as causes for stress in medical students (Yusoff et al.,
2013). General stress management was found to be helpful for reducing medical students’
stress (Dyrbye et al., 2017; Herizchi et al., 2016). Noting the effectiveness of stress
reduction, some medical schools have attempted to address medical students’ stress by
implementing stress management programs to help students cope and manage their stress
(Ebner et al., 2018). These programs have been either voluntary or required with many
being completed at the students’ will. Yet with stress management being available to
students, reports of moderate stress among medical students remained consistent (Dyrbye

2
et al., 2017; Yang et al., 2018). Because students’ stress levels remained moderate,
researchers have suggested that stress management resources that have been incorporated
into the curriculum would be the most beneficial for reducing medical students’ stress
rather than being provided to students as an option (Brennan et al., 2016; Pohontsch et
al., 2018; Scholz et al., 2016). However, the research was focused on allopathic (MD)
students’ stress levels instead of osteopathic (DO) students’ stress levels. Therefore, this
study was conducted to examine the effect of participation in a 4-week stress
management module on first-year DO students’ stress levels while they were enrolled in
the program. The intention of this study was to understand how stress management
resources that were incorporated into a DO program could help students’ stress levels
over time and impact a positive social change for students.
In this chapter, I will review the background of the study, the problem statement,
and the purpose of the study before stating the research question and providing the
theoretical frameworks that ground the study. Additionally, I will describe the nature of
the study, provide definitions applicable to the study, and identify the assumptions of the
study. Scope and delimitations are provided before limitations of the study are
acknowledged, followed by the significance of the study and a summary before moving
to Chapter 2.
Background
There is a wide variety of research related to stress management for medical
students. Some literature suggested that voluntary, or optional, stress management was
beneficial for students while other literature suggested that some form of stress

3
management training be implemented within the medical school curriculum to ensure
best practices and higher success rates (Abramova et al., 2015; Loh et al., 2022).
However, the need for preventive stress management efforts in medical schools remains
constant (Abdelsalam & Said, 2022; Loh et al., 2022).
In 2014, Saravanan and Wilks conducted a cross-sectional study to explore the
medical student experience and its correlation to stress through the use of stress scales
and found that stress-related factors decreased as students progressed through the medical
program. However, the authors noted that some students may have trouble overcoming
stressors without institutional assistance which could lead to the student performing
poorly academically, unhealthy coping behaviors such as turning to substance abuse, and
mental disorders indicating the need for action. Loh et al. (2022) conducted a randomized
controlled study on the effectiveness of a 4-week program for managing stress and found
mindfulness-based stress management programs successful for reducing medical
students’ stress levels. In their cross-sectional study on medical students’ stress levels,
Abdelsalam and Said (2022) used surveys to determine that high stress levels and poor
knowledge on how to effectively cope with stress contributed to high rates of depression
and suicide. The researchers suggested that stress management be embedded into the
curriculum to assist medical students by helping them manage the complexities
associated with medical school.
To combat the phenomenon of high stress levels among medical students,
researchers have studied potential effective coping mechanisms for students, including
peer-support programs and courses that teach proper stress management techniques

4
(Chung et al., 2018; Ebner et al., 2018; Herizchi et al., 2016). Researchers have indicated
that medical school itself is a stressor for students, and many have recommended that
institutions embed stress-management courses into their medical school curricula to
provide students the resources to manage their stressors at the source and offer students
the best opportunity to succeed as medical students and future physicians (Abdelsalam &
Said, 2022; Brennan et al., 2016; Chung et al., 2018; Kakoschke et al., 2021; Loh et al.,
2022; Pohontsch et al., 2018). Although research revealed techniques for managing
medical students’ stress levels to be beneficial for students’ well-being (Ayala et al.,
2018; Ebner et al., 2018), self-reports of moderate to high stress levels remained a
common occurrence (Abdelsalam & Said, 2022; Chung et al., 2018; Ebrahimi, &
Atazadeh, 2018; Loh et al., 2022).
Abramova et al. (2015) explored the different characteristics of anxiety,
depression, and stress based on the different stressors that occur at various stages in
medical education among medical students through a cross-sectional survey and found
that the high expectations placed on medical students to succeed, along with worry,
depression, and difficulty concentrating, contributed to their stress levels and often led to
students displaying symptoms of depression. In later research, Ehring et al. (2021) also
used a cross-sectional survey and found that medical students preferred to take an
elective stress management course as a means for helping their stress levels. Researchers
reported that when offered a stress management elective, students completing the elective
found the course to be useful for identifying and discussing stressors (Abramova et al.,
2015; Ehring et al., 2021). The results of these studies revealed the positive effects of

5
incorporating stress management courses into the curriculum to minimize the harmful
effects associated with medical education; and recommendations included encouraging
academic staff to increase awareness of stress and depression symptoms and provide
stress management techniques and social support to help students develop appropriate
coping skills (Abramova et al., 2015; Ehring et al., 2021). This research, however,
focused on MD students’ stress levels and did not acknowledge DO students’ stress
levels.
The gap in knowledge that I explored in the study was the effect participation in
stress management training on first-year DO students’ stress levels, specifically while the
students were actively enrolled in the program. This study was necessary to contribute to
the current knowledge found in the literature by adding a component that addressed how
stress management module participation affected DO students’ stress levels, an aspect
that had been minimally studied.
Problem Statement
Although studies show stress management to be beneficial for helping students
alleviate stress, few studies have been conducted with DO students as participants.
Research revealed that stress levels vary based on the year of medical school training
(Anandhalakshmi et al., 2016), and James et al. (2017) found that a variety of factors
influenced students’ stress levels. Erschens et al. (2018) noted that the highest stress
levels occurred during critical semesters and stages in medical school, and that it would
be beneficial to inform students about the high-stress stages in the curriculum and
incorporate stress management programs to prepare students for the stressors that may

6
present themselves during their medical school training. Although many institutions have
offered stress management programs for their students, the research focused on MD
students’ stress levels. The DO approach to medical care and treatment differs from the
traditional MD practice in that holistic practices are used to treat the patient versus the
traditional approach of solely treating the ailment (Bohlen et al., 2021; Grevitz, 2019).
Researchers indicated that general stress management has shown to be beneficial
for MD medical students in the long run (Dyrbye et al., 2017; Dyrbye, Thomas, et al.,
2010; Heinen et al., 2017), and it has been recommended that medical school faculty and
staff identify students with perceived high levels of stress and provide stress management
training in effort to lower stress levels and contribute to student success throughout the
program (Dagistani et al., 2016). Because studies focused on students enrolled in MD
programs and did not include students enrolled in DO programs, the gap in the research is
that there was little research published on DO students’ stress levels when provided stress
management resources, focusing on the first year of DO school.
Purpose
The purpose of the quasi-experimental study was to assess the effect of
participation in a 4-week stress management module on first-year DO students’ stress
levels. This study included two variables: DO students’ stress levels and participation in
the stress management module. DO students’ stress levels was the dependent variable
measured with the Perceived Stress Scale (PSS) before and after participation.
Participation in the 4-week stress management module represented the independent
variable. I developed one research question to guide the study.

7
Research Question and Hypotheses
One question has been presented for this research study:
RQ: What is the difference in first-year DO students’ stress levels as measured by
the PSS before and after they participated in a 4-week stress management module?
H0: There is no difference in first-year DO students’ stress levels as measured by
the PSS before and after participating in a 4-week stress management module.
Ha: There is a difference in first-year DO students’ stress levels as measured by
the PSS before and after participating in a 4-week stress management module.
Theoretical Framework
This study was grounded in Quick and Quick’s (1984) preventive stress
management theory and Bandura’s (1977) self-efficacy theory. With this foundation, I
explored the effect stress management training had on first-year DO students’ stress
levels. Quick and Quick’s theory of preventive stress management suggests that early
recognition of stress and implementing immediate measures to reduce and manage stress
are beneficial to the organization’s individual population as well as the collective unit.
Additionally, Bandura’s self-efficacy theory suggests that different coping mechanisms
can alter and sustain the strength of a person’s self-efficacy; suggesting that with
consistent behavior as seen in a modular course, self-efficacy is enhanced through
repetitive tasks and mastery of the content (Bandura, 1977). I applied both theories to the
study with an understanding that early acknowledgment and implementation, as well as
providing consistent stress management practices by incorporating a stress management
module while students were actively enrolled in the program, may be effective for

8
reducing medical student stress levels. Self-efficacy scales have been found effective for
understanding how people rate their circumstances to enhance perceived achievement
(Schunk & Pajares, 2002). Using the PSS, I sought to understand how early
acknowledgment of stress and consistent participation in a stress management module
affected DO students’ stress levels starting with the first year of enrollment in the
program.
Nature of the Study
In this research study, I used a quasi-experimental design to understand the effect
participation in a 4-week stress management module had on first-year DO students’ stress
levels based on presurvey/postsurvey data obtained from the PSS. The two variables for
the study included DO students’ stress levels as the dependent variable and the stress
management module representing the independent variable. All first-year students
enrolled in the DO program at the study site were asked to participate in the study. Study
participants were asked to complete the PSS as a presurvey assessment to capture
baseline data before a 4-week stress management module was implemented while
students were actively enrolled in the program. After the module ended, participants were
asked to complete the PSS to capture the postsurvey responses.
Definitions
The key terms associated with this study are defined below along with the
research behind several aspects of medical education that students have experienced, and
researchers have explored over the last decade. To enhance understanding, the key terms
are defined as follows.

9
Mindfulness: A term used to reflect self-awareness of one’s current emotional
state in an objective manner (Zhang et al., 2019).
Osteopathic medicine: A degree program – abbreviated as DO – that encompasses
a distinct practice of medicine founded on beliefs that medicine should treat the mind,
body, and spirit as one unit (Bohlen et al., 2021).
Quality of life: A person’s experience of their current condition in life based on
their physical, mental, and psychological health; and their ability to care for themselves
and maintain social relationships (World Health Organization Quality of Life Group,
1998).
Stress: A common feeling of mental tension which can produce nervousness,
physical pain, or negative psychological reactions in humans (Shahsavarani et al., 2015).
Stress may result in an emotional feeling of being overwhelmed, apprehensive, or
exhausted (American Psychiatric Association, 2014).
Stress level: The total level at which a person is experiencing signs of stress as
measured by the PSS (Cohen et al., 1983).
Well-being or wellness: A person’s ideal functioning in daily life complete with
personal satisfaction, achievement, and happiness (Cooke et al., 2016).
Assumptions
One assumption for the study was that DO students would complete the PSS
presurvey and postsurvey honestly to truly reflect on their currently perceived stress
levels and not be subjected to response bias. Additionally, since the stress management
module did not include guided exercises, another assumption was that the participants

10
would actually complete the stress management module exercises and not just report that
they did, contributing to an actual reflection of DO students’ stress levels after
participating in the module.
Scope and Delimitations
The scope of this study encompassed DO students completing their first year of
enrollment at a DO school in the southeastern United States to measure baseline stress
levels before the students became heavily involved in the more difficult curricular
components. Capturing the baseline stress levels for first-year DO students was a
necessary aspect of focus since research identified changes to medical students’ stress
levels throughout the medical school program. Additionally, with this study, I intended to
highlight stress levels among DO students - a field that had not been widely studied or
explicitly published.
Within the scope of this study, focusing on first-year DO students’ stress levels at
the start of their enrollment in the DO program aligned with Quick and Quick’s (1984)
theory of preventive stress management to understand how recognition of stress and
access to immediate stress management resources could help DO students manage their
stress levels. Combined with Bandura’s (1977) self-efficacy theory, this study aimed to
understand if consistent stress management behaviors could alter DO students’ self-
efficacy. The results of this study could be generalizable for other DO students
experiencing moderate to high stress levels and could potentially serve as a resource for
other DO programs that may be considering incorporating a stress management module
into the curriculum for their students.

11
Limitations
Limitations of the study sample included research that matriculating students were
already exhibiting higher stress levels compared to the general population due to
preparation for medical school (Anandhalakshmi et al., 2016). Additional research design
limitations included collecting data from one location and using only one group of
participants categorized as first-year DO students when other cohorts in the program
could have benefited from participating in a stress management module, minimizing the
generalizability of the study. Also, because there was minimal information available on
this specific topic, it was unknown whether the osteopathic principle of whole-body
practice influenced DO students’ mindset on stress and well-being. Exclusionary criteria
included students from different cohorts and first-year students enrolled in other
programs offered by the college. Additionally, because this study was concentrated on
students from one DO school, the results may not be generalizable for other medical
schools or for schools that offer multiple health professions programs. Ethical procedures
for collecting and reporting data were followed as reasonable measures to address these
limitations.
Lastly, the timing of the presurvey occurred during the start of the participants’
finals. I understood that if an effect in stress were to be revealed during data analysis, it
could be due to the timing in the semester and not necessarily related to the stress
management module. With this revelation, I took the time to incorporate a few
preliminary questions into the postsurvey introduction to capture module completion
before the participant could move forward and respond to the PSS postsurvey,

12
understanding that stress levels could possibly be inflated due to finals. Due to timing in
the semester, there was a small number of participants in this study, further contributing
to the study’s limitations. To address these limitations and garner more participants for
the study, the recruitment period was extended from 4 weeks to 10 weeks, and the
postsurvey remained available to participants for 2 weeks.
Significance
This study assessed the effect of participating in a 4-week stress management
module on first-year DO students’ stress levels. The stress management module was
optional for students but was incorporated into a course that students were required to
complete for the program. Studies have shown that participation in stress management
programs while enrolled in school have been effective for reducing and managing stress
(Heinen et al., 2017). Incorporating a stress management module into the medical school
curriculum may have the potential to reduce stress in medical students by providing
consistent stress management activities and techniques that students are required to
practice and contribute to student success and achievement by effectively managing
stress resulting in less burnout (Dyrbye, Power, et al., 2010; Dyrbye et al., 2019; Dyrbye
& Shanafelt, 2011). This research promotes positive social change by exploring the
effectiveness of stress reduction through participation in a stress management module and
ultimately supporting DO student success.
Summary
This study aimed to contribute to the field by adding knowledge on how DO
students’ participation in a stress management module affected their stress levels. The

13
study was grounded in two theories – Quick and Quick’s (1984) preventive stress
management theory and Bandura’s (1977) self-efficacy theory – that addressed the
importance of early recognition of stress, immediate stress management, and consistency
with practice to encourage effective coping and stress management through enhanced
self-efficacy. Because research showed that stress management was effective for medical
students and researchers have suggested that medical schools assist their students by
incorporating stress management into the curriculum (Abdelsalam & Said, 2022;
Lalithamma et al., 2022; Norphun et al., 2020), I assumed that a stress management
module that ran simultaneously to a required course could potentially be beneficial for
students. Medical students’ stress, and different aspects contributing to it, had been
commonly explored. However, literature was lacking on how participation in a stress
management module affected DO students’ stress levels.
In Chapter 2, I name the search strategies used to identify the literature applicable
to my topic. I also provide greater details on the two theories that supported this study as
well as the approaches and conclusions other researchers have reported on medical
students’ stress levels in the past. Additionally, I discuss the importance of addressing
medical students’ well-being, the research on medical students’ stress levels, and the
research designs other researchers have used to approach similar studies aimed at
facilitating medical students’ stress. Finally, I reveal the gap in the research that led me to
develop a study focused on the effect of a stress management module on first-year DO
students’ stress levels.

14
Chapter 2: Literature Review
This study focused on the effect of a stress management module on DO students’
stress levels. Although studies show stress management to be beneficial for helping
students alleviate stress, few studies have been conducted with DO students as
participants. The purpose of the quasi-experimental study was to assess the effect of
participation in a 4-week stress management module on first-year DO students’ stress
levels. Research shows that stress management has been effective for medical students,
and researchers have suggested that medical schools assist their students by incorporating
stress management into the curriculum (Abdelsalam & Said, 2022; Lalithamma et al.,
2022; Norphun et al., 2020). However, literature is lacking on how participation in a
stress management module affects medical students’ stress levels, specifically DO
students’ stress levels.
In this chapter, I review the literature search strategies I used to gather
information on the topic and provide information on the theoretical frameworks that
ground the study. I also synthesize the research into sections that include medical
students’ stress levels along with voluntary and involuntary stress management
conclusions other researchers have reported on medical students’ stress levels in the past.
Additionally, I discuss the importance of addressing medical students’ well-being, the
research on medical students’ stress, and the research designs other researchers have used
to approach similar studies aimed at facilitating medical students’ stress. Finally, I reveal
the gap in the research that led me to develop a study focused on the effect of a stress
management module on first-year DO students’ stress levels.

15
Student success and retention are common concerns for institutions of higher
education (American Association of Collegiate Registrars and Admissions Officers,
2016). An understanding of the student experience, which includes student factors and
the learning system, is needed as medical schools aim to contribute to student success
(Kahu & Nelson, 2018). Medical education is claimed to be lengthy and draining for
students, resulting in stress (Radcliffe & Lester, 2003). Although the definition of stress
may vary, many agree that stress occurs because of pressure combined with a lack of
resources to help manage and cope with the effect (Dhandapani et al., 2022; St. Hilaire,
2016). Moderate to high stress levels have been consistently identified as a problem for
medical students (Al Raddadi et al., 2017; Anandhalakshmi et al., 2016; Dyrbye et al.,
2017).
One study reported that numerous medical students have moderate levels of
stress, and that stress levels vary based on the year of medical school training
(Anandhalakshmi et al., 2016). James et al. (2017) found that a variety of factors
influence students’ stress levels; and as a result, nearly a quarter of the study’s
participants experienced depression and anxiety symptoms. Researchers have also found
that the highest stress levels seem to occur during critical semesters and stages in medical
school and noted that it would be beneficial to inform students about the high-stress
stages in the curriculum (Erschens et al., 2018). Simultaneously, Erschens et al. (2018)
suggested that medical schools incorporate stress management programs to prepare
students for the stressors that may present themselves during their medical training.

16
Research showed stress management to be an efficient method for helping
medical students cope with stress (Norphun et al., 2020). Additionally, voluntary stress
management programs have been found to be helpful for reducing stress in medical
students (Wiles, 2015), yet students continue to report experiencing average to high
levels of stress (Al Raddadi et al., 2017; Anandhalakshmi et al., 2016). Stress has also
been linked to feelings of burnout which could increase a student’s chance for not
completing the program (Dyrbye et al., 2019; Zisook et al., 2016). It is important to
ensure effective preventive and stress management training is available to students as an
academic support resource which leads to success in the program and ultimately as
physicians.
Given the research on the effectiveness of stress management for reducing
medical students’ stress levels, the purpose of the quasi-experimental study was to assess
the effect of participation in a 4-week stress management module on first-year DO
students’ stress levels. The following literature review details the past few decades of
research on medical students’ stress, contributing factors to medical students’ stress, and
the importance of maintaining mental health and well-being as related to medical
education, training, and practice as future physicians.
Stress is found to be common among medical students (Dahlin et al., 2005;
Dyrbye et al., 2017; Goebert et al., 2009). There are different periods during medical
training that studies have shown affect students’ stress levels (Kukade et al., 2016; Slavin
et al., 2014). Research has found stress management to be effective for medical students
(Dyrbye, Power, et al., 2010; Heinen et al., 2017). Researchers noted that although stress

17
management programs may be available for medical students, there remains a need to
review the medical school curriculum to understand how stress management programs
can be integrated into the curriculum to help students manage their stress levels
effectively (Chung et al., 2018; Polle & Gair, 2021).
Yusoff et al. (2013) showed stress management to be an effective tool for
reducing medical students’ stress levels. Studies have been conducted to examine the
effectiveness of stress management programs in medical schools for managing students’
stress levels (Polle & Gair, 2021; Verweij et al., 2018). Although voluntary stress
management programs have been found effective for reducing medical students’ stress
levels, mandatory stress management programs have been found more effective for
maintaining lower stress levels (Polle & Gair, 2021; Slavin et al., 2014). Given the nature
of the mandatory sessions, it is understood that the continuous and repetitive techniques
identified in the sessions are what make required stress management programs so
effective (Saleh et al., 2017).
The method for implementing stress management programs has varied throughout
the literature. For example, Ayala et al. (2018) and Kushner et al. (2011) conducted their
stress management studies using qualitative methods while others, like Radcliffe and
Lester (2003) and Jordan et al. (2020), chose quantitative routes for exploration.
Regardless of the method. However, one common factor exists: the goal was to
understand more about how to effectively reduce medical students’ stress levels while in
training (Ayala et al., 2018; Dyrbye et al., 2017; Radcliffe & Lester, 2003). The
commonly used scales have been shown effective for determining perceived student

18
stress (Gadzella et al., 2012; Lonka et al., 2021). However, a variety of methods for
implementing stress management programs have been found to be effective, with the
most effective for reducing and maintaining stress levels being platforms that integrate
well within the curriculum or are easily accessible, including platforms such as social
media or cellular applications (Henning et al., 2011; Yang et al., 2018).
Literature Search Strategies
The literature search strategies were broad in the beginning stages of the literature
review. With the initial search, I began with searching for stress in medical school or
medical students using the Walden Library’s EBSCO search database to identify peer-
reviewed articles on the topic. From there, I sorted the results by narrowing the search
field to incorporate recent articles published within the last 5 to 15 years and scanned
through article titles and abstracts potentially related to the study. The seminal literature
that populated in my search results were important for laying the foundation of how
frequently medical students’ stress levels has been studied, resulting in older dated
articles. I quickly identified several peer-reviewed articles written by the same author
about medical students’ stress levels and preventing stress in medical students. I noted
that the author Dyrbye would be a prominent resource for the literature review due to the
number of relevant publications. I also began to search Google Scholar for “stress
management programs in medical schools” and “stress management for medical
students” with similar search parameters as initially set in my Walden searches and set
email alerts on the criteria to report more current research once published. As I got deeper
into the research, I continued to search the EBSCO database for more detailed topics and

19
themes commonly found in formerly reviewed articles, specifically related to medical
students and the medical school curriculum but now including search terms like
“mindfulness,” “well-being,” and “preventive stress management,” as they were all
seemingly connected based on the research. Eventually, I began to search education and
health science journals as well as education databases to yield more of the targeted
results. The higher education database searches led me to ERIC, ProQuest and SAGE
Publications, while I narrowed my search to discipline-specific journals leading me to
Academic Medicine, BMC Medical Education, Cognitive Therapy and Research,
Education in Medicine Journal, International Journal of Biomedical and Advance
Research, International Journal of Stress Management, and Medical Education as
recurring resources.
As time progressed, I started to notice that I was coming across the same articles
with my search procedure only yielding two or three new articles as my keywords
changed every week to incorporate something else that I found from a recent review. At
this point, I began to search retroactively using references from the most prominent
articles related to the study. I found several articles, although dated, that were applicable
to the study - all justifying the need for more research focusing on stress management in
medical schools or the need to identify effective ways to reduce stress/stressors in
medical students. These articles supported the foundation of my study better than the
more current research, which seemed to focus more on seminal reviews of the literature
rather than conducting new research. I also began to sort through the Google Scholar
alerts I received. I found that I had reviewed those articles found through the EBSCO

20
searches I previously conducted, so I continued to monitor the alerts to ensure I captured
all that was related to the study and verify I had reached saturation on the topic. Although
the seminal and peer-reviewed articles I identified early-on were a little dated, I found
them to be key references to incorporate into the literature review and throughout the
study to show the history on the topic that allowed me to identify the gap in the literature.
Theoretical Frameworks
Aiming to explore the effects of participating in stress management training on
DO students’ stress levels, this study was grounded in two theories: Bandura’s (1977)
self-efficacy theory and Quick and Quick’s (1984) preventive stress management theory.
Bandura’s self-efficacy theory suggests that coping techniques can alter and sustain the
strength of an individual’s self-efficacy. This theory also suggests that with consistent
practice, self-efficacy is enhanced through repetitive tasks and the ultimate mastery of the
content (Bandura, 1977). Quick and Quick’s theory of preventive stress management
suggests that early recognition of stress along with the early implementation of measures
to reduce and manage stress are considered beneficial to individuals within an
organization as well as the collective organization population. Together, these two
theories have been applied to the study with the general understanding that early
acknowledgment and implementation, as well as requiring consistent stress management
practices by embedding stress management modules into the curriculum, may potentially
affect medical students’ stress levels.

21
Bandura’s Self-Efficacy Theory
Bandura’s self-efficacy theory (1977) lays the primary foundation for the
theoretical framework, which explains how one may anticipate the psychological changes
related to stress after exposure to different types of treatment. The theory suggests that
self-efficacy can be altered and strengthened through different procedures. Self-efficacy
could be used as a vital tool for determining whether coping mechanisms will be initiated
and determining whether the effort will be extended and sustained when faced with
obstacles or adversities (Bandura, 1977). Persistence through activity along with mastery
of content are said to enhance self-efficacy and reduce defensive behavior. Self-efficacy
is also generated from accomplishments, experiences, persuasion, and physical
symptoms. The more reputable the source, the greater the changes in perceived self-
efficacy are said to be (Bandura, 1977).
To further develop his theory, Bandura (1978) evaluated the processes that had
been identified as contributing factors to one’s self-efficacy. From this evaluation, it is
understood that psychological functioning requires a person to continuously evaluate
their responses to social and emotional changes. Arguments on human behavior and self-
efficacy evolve around the issue of one’s perceived self-influences, drive, and
determination. In reciprocal determinism, the self-system provides an important
component to self-regulatory processes by providing the individual with an introspective
position on the situation, and it is a basic principle for how one evaluates and responds to
their personal development, social interactions, and when working in an organization
(Bandura, 1978). A couple of years later, Bandura tested the predictive generality of the

22
self-efficacy theory and found that self-efficacy supports the social learning concept in
terms of perceived coping (Bandura et al., 1980).
Supporting Bandura’s Theory
Supporting Bandura’s self-efficacy theory, Guntern et al. (2017) noted that a
person’s character and personality can improve how well they will perform academically.
The researchers conducted a study that expanded on former research by addressing how
self-efficacy can serve as an indicator of perceived academic achievement. The
researchers used a questionnaire to measure personality characteristics, adjusting the
questions to the medical context. The self-efficacy scale was added to assess students'
self-confidence. The researchers examined the connections between predictors for self-
control, emotional stability, self-efficacy, and being social. Results showed that the
connections among predictors were moderate, but the connection between emotional
stability and the student’s self-efficacy was particularly high (Guntern et al., 2017).
Jackson (2002) found that a student’s self-efficacy beliefs are significantly related to
overall performance.
O’Leary (1992) found self-efficacy to be a determining factor for behavioral and
emotional processes. The author identified two paths for self-efficacy that influence
health: one is its effect on embracing behaviors related to health, and the other deals with
its role in the physiological response to stress, which affects health independent of health
behaviors (O’Leary, 1992). Henning et al. (2011) conducted a study where the
researchers surveyed 274 medical students enrolled in their 4th and 5th year of medical
school (clinical studies) at the University of Auckland. The results showed that the

23
quality-of-life indicators were directly related to self-efficacy. The authors noted that
well-being and the medical school experience interact with each other, and a holistic
design for medical education should consider the whole student as body, affect,
cognition, and behavior. Motivation to learn and quality of life should be integrated into
the curriculum since these factors are directly correlated with academic achievement
(Henning et al., 2011). Furthermore, the authors suggested discussions and interventions
be integrated into the curriculum, with a focus on quality of life and motivation to learn
to optimize learning outcomes.
Responding to the observation that many learners struggled with their studies due
to low self-efficacy, Margolis and McCabe (2003) conducted a study to identify methods
in which teachers could help strengthen struggling learners and found that the key is for
educators to reverse students’ perceptions of learning by stressing the importance of
developing high self-efficacy to promote student success. Yildirim and Alanazi (2018)
examined the relationship between a person’s perceived stress and life satisfaction and
the effects it has on self-efficacy among college students in Saudi Arabia. Using the PSS,
the Satisfaction with Life Scale, and the Self Efficacy Scale, the researchers found that
life satisfaction and the student’s perceived stress had a mediating effect on the student’s
self-efficacy. Ebner et al. (2018) also found self-efficacy effective for serving as
mediation for stress management. The results of these studies supported the use of self-
efficacy as a means for intervention (Ebner et al., 2018; Yildirim & Alanazi, 2018).
Using Bandura’s self-efficacy theory (1977) as a theoretical framework will provide an

24
understanding of how medical students’ self-efficacy may be altered with consistent
practice of stress management techniques.
Quick and Quick’s Preventive Stress Management Theory
Quick and Quick’s (1984) preventive stress management theory provides the
supporting framework by identifying the importance of understanding that exposure to
stress is what triggers a stress response which may be managed once recognized.
Stressors may be environmental or self-imposed, but the final response to stress leads to
an outcome (i.e., fight or flight response). There are three stages of intervention: primary
intervention – which attempts to reduce the triggering stressors, secondary intervention –
which attempts to manage the person’s response to stress, and tertiary intervention –
which is aimed at controlling the final outcomes related to stress (Hargrove et al., 2011).
The preventive stress management theory notes that there can be many stressors
including role factors, job stressors, and interpersonal stressors. In support of the theory,
researchers also note that not all stressors have an effect nor do different stressors result
in the same response (Hargrove et al., 2011). Hargrove et al. (2011) suggested that
organizations assess stress as a means of preventive management. Interventions may take
different forms as identified by individual stressors, response to stress, and structure of
the organization (Hargrove et al., 2011). In former research, Quick and Quick’s (1984)
preventive stress management theory has been used to identify contributing factors that
led to stress, whether occupational or organizational (Quick & Henderson, 2016).
Following the preventive stress management theory, Quick and Henderson (2016) noted
that to effectively address how a person responds to stress, one must understand the

25
primary cause of stress, the individual’s reaction to stress, and understand the individual
differences that may have an underlying effect on the person, resulting in additional
stressors. Adding Quick and Quick’s preventive stress management theory to the study as
a supporting framework supports the effort for recognizing stress during the early stages
of medical education and implementing appropriate measures to reduce and manage
stress properly.
With Bandura’s self-efficacy theory (1977) and Quick and Quick’s (1984)
preventive stress management theory set as the foundation for my study, it is important to
understand why both theories served as the frameworks for introducing a stress
management module as a preventive tool to help DO students’ stress levels. The
following sections detail the prevalence of medical students’ stress, the factors associated
with medical students’ stress, and the importance of acknowledging and addressing
medical students’ mental health and well-being.
Medical Students’ Stress
A common theme found in medical schools is medical student stress (Norphun et
al., 2020). Medical students’ stress has been associated with several factors including the
stress of moving away from family, the pressure to do well, and curricular stress (Dabrow
et al., 2006). Over the years, many institutions have acted in response to this phenomenon
by offering stress management programs for their medical students (Yusoff et al., 2013).
However, medical students continue to report significant stress levels – even when stress
management resources are readily available to them (Greeson et al., 2015). Most stress
management programs have been voluntary for students, while only a few have been

26
required (Henning et al., 2011; Kar et al., 2015; Yang et al., 2018). Program types have
varied over the years, some being found more effective than others for decreasing
medical students’ stress and maintaining low stress levels (Dyrbye et al., 2017; Greeson
et al., 2015; Kar et al., 2015).
Medical Students’ Stress Compared to General Population
Several studies indicated that medical students tend to experience higher stress
levels than seen in the general population (Daskivich et al., 2015; Saleh et al., 2016;
Slavin et al., 2014). Researchers have also found that medical students consistently
display depression and stress rates higher than the general population (Slavin et al.,
2014). Researchers have noted that the high prevalence of stress and depression affects
academic performance and professionalism, both of which are two major competencies
for medical students (Yang et al., 2018).
Slavin et al. (2014) found that matriculating medical students tend to display the
same stress levels as seen in the general population but noted that stress levels seemed to
increase after students began medical school – indicating that the medical school
curriculum may be the reason behind the phenomenon. Yet, few studies have reviewed
initiatives that were developed in response to the negative effects seemingly associated
with medical school (Slavin et al., 2014). Brazeau et al. (2014) argued that from the
competitive application process and high demand to submit a strong application, it was
easy to see how matriculating medical students could be at a disadvantage for
experiencing higher stress levels or feelings of burnout compared to the general
population. From this viewpoint, the researchers considered that if students entered

27
medical school with comparable mental health compared to the general population that
changed once enrolled in medical school, the concerns about medical school training
having a negative impact on one’s mental health would be valid (Brazeau et al., 2014).
Additionally, physicians in training (i.e., residents and fellows) have been found to be at a
higher risk for depression while practicing physicians have an increased risk for suicide
compared to the general population (Daskivich et al., 2015). Based on these findings, it
appeared that certain stages in medical education produced more stress than others -
stages that are not typically experienced in the general population.
Regardless of the medical education stage, stress had still commonly presented
itself in multiple forms among medical students (Dyrbye et al., 2013). Dyrbye et al.
(2013) identified 62 possible combinations of stress observed amongst medical students
with the most common being reported as stress with burnout, exhaustion, high anxiety,
depression, and a low quality of life. Further research showed that depression and anxiety
were most common in medical students during their final year of training compared to
computer science students at the same stage (Al Raddadi et al., 2017). Although Dyrbye
and Shanafelt (2011) found that medical students tended to display a higher prevalence of
depression and suicidal ideation compared to the age-matched population due to stress, it
is important to note that this trend of stress seems to follow medical students beyond the
4 years of medical education and into resident training. After two separate incidents of
resident physicians’ death by suicide occurred in New York City, Daskivich et al. (2015)
found that practicing medical professionals have consistently shown higher suicide rates
compared to the general population.

28
It is also important to note that the scope of medical students’ stress compared to
the general population does not appear to have many geographical restrictions. In an
international study, Bramness et al. (1991) found that medical students in the United
States and United Kingdom report higher mental health symptoms than the general
population. Additionally, Agarwal et al. (2020) found the prevalence of stress and
perceived stress high among 200 first-year Saudi Arabian medical student participants.
Agarwal et al. (2020) found that students with a proficiency to recognize their emotions
seemed to have had a better ability to manage their stress. Understanding that stress can
affect student performance, the researchers indicated that enhancements to the curriculum
as a means of providing resilience training could be helpful for reducing medical
students’ stress (Agarwal et al., 2020).
Brazeau et al. (2014) also noted that despite a high prevalence of stress and a
limited understanding of how stress can result in serious personal and professional
problems, there was still little known about what to do in response to the stressors that
medical students experience. To assist with this, many researchers suggest specific
wellness and mental health resources tailored to the medical school experience (Agarwal
et al., 2020; Daskivich et al., 2015; Dyrbye et al., 2013). Noting that quick identification
of high-risk students is necessary for effective well-being programs along with regular
screening to capture students who have developed strong risk factors, Dyrbye et al.
(2013) suggested that stress management programs that focus on promoting well-being
incorporate a comprehensive and rigorous approach to justify the need for wellness and
support programs for all medical students during their medical school training. Daskivich

29
et al. (2015) added that graduate support resources were limited or lacked the depth to
adequately support residents in training.
Stress, in general, is also a common occurrence throughout the literature and
transpires globally. Hathaisaard et al. (2022) conducted a review and meta-analysis on
mindfulness-based interventions and found that several studies showed an increased risk
for psychological disorders in medical students. Researchers also found that compared to
the general population, burnout and low physical and mental health prevailed among
physicians (Hathaisaard et al., 2022). Scholz et al. (2016) also found that medical
students are at a higher risk for developing stress-related symptoms – such as burnout,
anxiety, and depression. Yang et al. (2018) found that medical students experience higher
rates of depression and stress compared to the general population, which in turn, affected
academic performance and professionalism, indicating that a need to address the problem
remains.
Factors Associated With Medical Students’ Stress
Because medical students have identified stress as a common occurrence during
their medical training, it is important to identify and address the factors that may be
considered as triggers for inducing stress (Dyrbye, Power, et al., 2010). Medical schools
should be aware of the factors that contribute to medical students’ stress when addressing
the phenomenon and tailoring programs to help students manage their stress (Goebert et
al., 2009). Research shows that stress-related factors may be personal (i.e., worries about
the future and financial troubles) or professional (i.e., heavy workload and lack of
professional resources) and vary in nature (Hargrove et al., 2011; Norphun et al., 2020;

30
Yusoff et al., 2013). However, students can benefit from understanding these factors by
proactively addressing them immediately before the start of the program or through stress
management techniques while enrolled (Ebrahimi & Atazadeh, 2018; Kukade et al.,
2016).
Although a wide range of personal and professional factors can influence a
student’s well-being, researchers have found that student satisfaction and success with
specific characteristics of the learning environment are critical (Dyrbye et al., 2009). To
understand how coping responses are linked to stress, self-efficacy, motivation, and other
traits, Li and Yang (2009) conducted a study and found that the effect of stress could be
mediated by self-efficacy. In turn, Seedhom et al. (2019) found that students with mild to
moderate stress were more likely to experience the physical symptoms associated with
stress. The authors noted that institutions would need to take action to improve student
well-being (Seedhom et al., 2019).
Studies also showed a variety of factors related to medical students’ stress, and it
was noted that understanding which factors are most common is pertinent for structuring
student wellness programs (Dyrbye et al., 2013; Kushner et al., 2011). Common factors
include the stress of the transition into medical school, the medical school curriculum, the
grading schema of medical school, and pressure to do well (Dyrbye & Shanafelt, 2011;
Dyrbye et al., 2006; Slavin et al., 2014). Additionally, poor learning, low academic
performance, homesickness, language barriers, and exam frequency have been identified
as stress-causing factors for medical students (Dhandapani et al., 2022). In addition,
being on a hospital rotation or an overnight on-call rotation were identified as other

31
stressors leading to burnout (Dyrbye et al., 2009). A study conducted by Dyrbye et al.
(2006) revealed that medical school presents a detectable personal stressor for medical
students and should not be disregarded as a primary source, and Brazeau et al. (2014)
supported the finding that medical school may potentially have a negative impact on
medical students’ stress and well-being.
Additionally, motivation has been directly linked to students’ well-being (Aulia et
al., 2020). Researchers found that if students perceived the instructor as a leader, helpful,
and friendly, they tended to score higher on well-being assessments, suggesting that
positive and helpful interactions between instructors and students motivated students to
learn and continue to want to learn (Aulia et al., 2020). Yusoff et al. (2013) also argued
that the training for medical school was counterproductive, as it seemed to promote a
suboptimal learning environment and psychological being for medical students. Dyrbye
et al. (2013) found the most common stressors among medical students were associated
with burnout, exhaustion, high anxiety, depression, and a low quality of life which were
also connected to thoughts of dropping out from the program. The researchers
emphasized that the higher the amount of stress indicators reported, the higher the odds
of having suicidal thoughts or serious thoughts of not completing the program (Dyrbye et
al., 2013). To counteract the effects of a suboptimal learning environment, Aulia et al.
(2020) suggested the concept of having faculty build more personable relationships with
students and display an earnest interest in students’ well-being to serve as a benefit for
decreasing stress, minimize the risk of burnout, and dropping out typically seen in
medical students.

32
When measuring stress and anxiety at the start of medical training, researchers
found an increase in anxiety, stress, and depression scores (Yusoff et al., 2013). Other
transitional periods (i.e., from second year to clinical training, clinical training to
graduation/residency), exam frequency, study time, and difficulty adjusting to change
were also identified as potential stress factors for medical students as were being sick,
injured, or setting expectations too high (Dhandapani et al., 2022; Kushner et al., 2011).
Students have also identified comprehensive exams, attendance requirements, internal
motivation, the first medical exam, and medical responsibility as the main stressors
(Pohontsch et al., 2018). Lack of support from the medical school faculty and
administration were also identified as potential stress factors for medical students
(Dyrbye, Thomas, et al., 2010; Radcliffe & Lester, 2003). Marital status, confidence, and
self-esteem also serve as influential factors that affect stress levels among medical
students (Bramness et al., 1991). Although stress seemed to be more prominent in female
medical students, little was known about demographic variables as stress-causing factors
(Dyrbye et al., 2006). However, researchers have found some of the most important
stressors to be curriculum-related, which suggests that implementing practices in medical
schools that train students to become aware of stress and learn to cope with it may be
needed within the curriculum (Pohontsch et al., 2018).
The Importance of Medical Students’ Mental Health and Well-Being
The primary goal of medical education is to educate skilled and professional
physicians to care for the sick and to improve science in medicine (Dyrbye et al., 2006).
Hafferty and Franks (1994) noted that the most critical elements for physician identity are

33
not found within the formal curriculum but instead are hidden within the informal
curriculum. Additionally, the high levels of stress and depression reported by medical
students were particularly concerning, especially since the literature revealed that these
levels affected academic performance and professionalism (Yang et al., 2018). Mental
health and well-being are important components for existence and livelihood, in general,
but it appeared these two aspects were critical for physicians in training. Higher mental
health symptoms were reported for medical students in the United States and United
Kingdom compared to the general population (Bramness et al., 1991). Burnout had also
been commonly identified as a problem for medical students which could lead to
thoughts of dropping out of the program or suicidal ideation (Dyrbye, Power, et al., 2010;
Dyrbye et al., 2019). In a 2013 study on medical students’ stress, over 80% of
participants reported experiencing at least one form of stress (Dyrbye et al., 2013).
Overall, high stress levels during medical training negatively affect medical
students' mental health (Ruzhenkova et al., 2018). Burnout and mental disorders in
medical students tend to increase as scholastic stress develops, affecting medical students'
quality of life. Ruzhenkova et al. (2018) mentioned that students would sometimes resort
to the use of various substances (i.e., the use of cigarettes and alcohol) as a method to
cope with stress. Additionally, researchers noted that the burnout levels that medical
students have reported imply that there may be consequences that affect medical
students’ attitudes, behaviors, and emotions, suggesting that increasing levels of burnout
related to their occupation of choice resulted in decreased professionalism (Ebrahimi &
Atazadeh, 2018; Ruzhenkova et al., 2018). The consequences, in turn, may potentially

34
affect commitment to professionalism as physicians (Ebrahimi & Atazadeh, 2018;
Ruzhenkova et al., 2018).
Stress has been found to be an extremely common occurrence during the first year
of medical school training (Carson et al., 2000). However, Yang et al. (2018) found that
stress directly affects medical students’ professionalism, a competency objective required
throughout the program and necessary for success as practicing medical physicians.
Thomas et al. (2007) emphasized that professionalism is a multi-faceted competency for
medical students with many categories that relate to how well students score on
competency exams, suggesting that well-being may be correlated to professionalism.
Tarchi et al. (2021) pointed out that the frequency of depression and suicidal ideation
among medical students who report poor mental health throughout medical school
training and do not seek appropriate care may be due to the stigmatization surrounding
the topic, leading to suicidal ideation and thoughts of dropping out. Medical students
have said the stigma of depression and reporting their depression or seeking assistance
felt as if it would be looked down upon by their peers (Tarchi et al., 2021). Being that
physicians typically tend to prioritize patient care over self-care (Kushner et al., 2011),
supporting research showed that residents and practicing physicians suffered from
burnout that originated in medical school (Dyrbye et al., 2006).
In fact, fellows and residents were found to be at an increased risk for suicide and
depression due to a lack of wellness resources available to them during that stage of
training (Daskivich et al., 2015). Dyrbye et al. (2006) felt that the medical education
system should consider the health and well-being of their students to improve medical

35
education; and with early acknowledgment and continuous stress management, medical
students, residents, and fellows could benefit from such resources. Residents participating
in mindfulness-based stress reduction programs reported feeling more accepting of
themselves and their personal weaknesses and mentioned the training helped them
become more resilient by providing an increased skill to help them set priorities and
boundaries (Verweij et al., 2018). The students’ ability to acknowledge their own health
issues has been found to be helpful for promoting credibility as future physicians and
potentially increases care for patients (Ruzhenkova et al., 2018). Participation in these
types of programs has also shown an increase in the sense of compassion for others
which further supports the need for prioritizing medical students’ well-being as it relates
to their professionalism (Verweij et al., 2018). Furthermore, Dyrbye et al. (2019)
emphasized the need for school-sponsored well-being activities to help support the
medical field’s professionalism competency standards that all board-certified physicians
are required to meet.
Stress Management Programs and Interventions for Medical Students
Former research revealed that medical student participation in stress management
programs has been helpful for decreasing depression and anxiety, increasing spirituality
and empathy as well as improving knowledge of stress effects with the use of positive
coping techniques and conflict resolution skills (Kukade et al., 2016). Seeing that many
medical students reported medium to high levels of stress, several programs have
identified stress management resources and made them available to students (Dyrbye et
al., 2017; Yang et al., 2018). Some medical students have reported substance abuse as a

36
means of coping (Dhandapani et al., 2022). Yusoff et al. (2013) supported the belief that
medical training is harmful to students’ psychological health. The curriculum and desire
to be the best student are heavy burdens on students when there are inadequate
intervention programs available to help them cope with this stress. The highest stress
levels were shown at the start of medical training and at the final examination period
(Yusoff et al., 2013). Researchers suggested that medical schools create strategies and
programs appropriate for their student population to prevent the short and long-term
effects of depression related to personal and professional development (Dyrbye et al.,
2006; Shapiro et al., 2000).
In response to the high prevalence of depression and suicidal ideation reported by
medical students in comparison to the age-matched population, Dyrbye and Shanafelt
(2011) noted that it is the medical school’s responsibility to encourage student wellness
beyond the basic teaching of self-care and suggested that cognitive-behavioral
approaches help students identify a behavior for improvement, monitor it, learn more
about it, and set personal goals to implement a support plan. Dyrbye and Shanafelt (2011)
also suggested that medical schools consider monitoring students’ emotional and mental
health, referring them to mental health providers outside of the institution if needed.
Because of the stress related to medical school training, burnout and poor physical and
mental health tends to prevail among physicians (Hathaisaard et al., 2022). Dhandapani et
al. (2022), however, added an important note regarding medical school stress:
Stress is an inevitable and important part of being a student: It motivates and
stimulates learning. However, intense stress can arouse feelings of fear,

37
uselessness, anger, incompetence and guilt. If it is not managed correctly, stress
can lead to high levels of depression, substance abuse, relationship problems,
anxiety, and suicide. (p. 2)
Although research reveals stress as a common phenomenon for medical students to
experience, Dhandapani et al. (2022) suggested that an appropriate level of stress is
actually needed in the competitive medical school environment, and the underlying issue
at hand is how students cope with that stress.
It is important to recognize that stress management programs offered to medical
students while enrolled in medical school have taken many forms including offering
yoga/meditation practices, general stress management group sessions, social media
platforms for delivering stress management practices, and the use of cellular apps to
promote stress management and well-being (Polle & Gair, 2021; Yang et al., 2018;
Yusoff et al., 2013). Kukade et al. (2016) found that students participating in yoga
exercises reported a better sense of well-being, improved concentration, self-confidence,
relaxation, increased attentiveness, and a lowered sense of irritability. Anxiety levels
were also reduced, prompting the researchers to validate it as a preventive approach to
incorporate into the medical school curriculum to allow medical students to adopt and
maintain positive health and eventually communicate these practices to patients and
promote a healthy lifestyle within the community as they serve as physicians (Kukade et
al., 2016). Finding burnout and fatigue as common presentations among medical
students, some researchers also searched for mindfulness-based intervention programs
specifically tailored to medical students to address stress, depression, burnout, and fatigue

38
(Daya & Hearn, 2018). Additionally, programs that are considered convenient and brief
resources, including offering mindfulness-based stress reduction techniques offered
through DVD, have been determined to be effective for medical school students and
suggested to be integrated into the curriculum (Greeson et al., 2015; Kar et al., 2015).
Milic et al. (2019) agreed that institutions should be attentive to how the curriculum is
developed to allow for proper stress management mechanisms to be formed and to
motivate students to use the resources offered to them. Overall, there have been mixed
reviews regarding the effectiveness of interventions to support medical students’ stress
management. However, it is still important to have a resource in place, whether voluntary
or involuntary, to help medical students manage stress and possibly prevent depression
(Daya & Hearn, 2018).
Voluntary Stress Management Programs
Medical education has been found to have a negative effect on students’ mental
health (Dyrbye et al., 2006). Researchers have found general stress management to be
effective for reducing medical students’ stress (Dyrbye et al., 2017; Herizchi et al., 2016).
Studies have been conducted to understand how stress management affects stress levels
in medical students (Brennan et al., 2016; Herizchi et al., 2016). Seeing the positive
effects of stress management on medical students’ stress levels, some institutions have
implemented stress management programs or interventions for students (George et al.,
2013; Greeson et al., 2015). These programs have been voluntary for students who
wanted to participate and recommended to students who deemed themselves “high risk”
(Dagistani et al., 2016; Dyrbye et al., 2013).

39
Voluntary stress management programs have been studied with different
platforms to promote stress management and well-being. Zetterqvist et al. (2003) utilized
stress management treatment interventions that were provided through the internet and
found the internet effective for providing stress management techniques that result in
stress relief. A decade later, George et al. (2013) conducted stress management using
Facebook, a social media platform, to guide students through the program and offer
resources in a manner that was fun, enticing, and unlike the curriculum delivery. The
authors found this method to be extremely beneficial for engaging student participation
since they were already using social media as an escape from studying, and it seemed less
burdensome and more like a close-knit community during participation (George et al.,
2013). It is essential to note that guidance is important but not the most important factor
in internet-based interventions (Baumeister et al., 2014). Cost-effectiveness should be
examined as an outcome as well as participant satisfaction. Unguided interventions
typically have lower initial costs and may be effective for increasing prevention of mild
disorders (Baumeister et al., 2014).
Dabrow et al. (2006) revealed that many institutions have already developed
stress management programs for their residents to assist with and combat stress. Parsons
et al. (2022) noted that mindfulness training was proving to be helpful for reducing stress
in health professions students and suggested that self-administered interventions to
manage stress in an at-risk population - such as medical students - should be used
(Parsons et al., 2022). Yang et al. (2018) used a cellular app called Headspace - a mobile
narrated mindfulness and meditation program - to promote stress management,

40
meditation, and well-being in medical students and found it to be effective for decreasing
stress and promoting mindfulness. Due to the success of the program, the researchers
suggested integrating mindfulness training into the medical school curriculum for
managing school and work-related stress, which may lead to fewer feelings of burnout,
anxiety, and depression as a physician (Yang et al., 2018). Daskivich et al. (2015) also
suggested medical schools incorporate an ideal learning environment for students at the
beginning stages of medical education to support students. For students, the ideal learning
environment would involve acknowledging the risk of depression and addressing this risk
to avoid stigmatizing it. Additionally, a formal mentoring process and having confidential
mental health services available within a supportive learning culture were also identified
as components of an ideal learning environment for the medical student (Daskivich et al.,
2015).
The fact that high stress levels have continuously been reported among medical
students has not gone unnoticed over the years. Yet, few intervention studies have been
conducted and even fewer have been conducted with the students' concern of time
constraints incorporated into the study. Greeson et al. (2015) conducted a prospective
observational study lasting only 4 weeks with a focus on developing mind-body skills
and found that short, voluntary programs prompted improvement in perceived stress,
mindfulness, engagement for self-care, and an understanding of stress management and
relaxation skills without altering the effectiveness. This program was found to be low-
cost, brief, and was shown to be efficient and effective for reducing stress in medical
students (Greeson et al., 2015). Similarly, Kar et al. (2015) conducted and evaluated a

41
5-week DVD-delivered mindfulness-based program adapted from the principles of the
8-week Mindfulness-Based Stress Reduction and Mindfulness-Based Cognitive Therapy
programs but found small outcome measures between variables. The researchers’
analysis showed significant improvements in the intervention group for perceived stress
and mindfulness but no actual changes in self-efficacy scores (Kar et al., 2015).
Several different types of interventions have been developed to help medical
students cope with elevated stress levels. Mindfulness-based interventions – have been
shown to reduce stress, anxiety, and symptoms of depression, even when as short as a
4-week program (Loh et al., 2022). Elective courses that focus on relaxation techniques
have also been found to be effective for improving medical students’ mental health by
improving burnout and anxiety levels (Hathaisaard et al., 2022; Loh et al., 2022). Scholz
et al. (2016) suggested integrating similar programs into the medical school curriculum to
acknowledge the prevalence of stress disorders in medical schools. Similarly, Hathaisaard
et al. (2022) agreed that a short voluntary extra-curricular activity showed a positive
effect of the interventions on the stress of coping strategies for medical students.
However, Loh et al. (2022) suggested that it would be best to embed voluntary
intervention sessions into an email format or use social media platforms that are popular
with medical students to promote efficacy and long-term use.
Ultimately, researchers urge medical schools to provide some form of a stress
management program for students to participate in. When institutions create mental
health programs for students, the importance of preventing mental health issues in the
student population is seen and appreciated by the students (Saleh et al., 2016). However,

42
research has found that wellness programs available to medical students may not be the
most beneficial for students who are already at risk (Brennan et al., 2016). For this
reason, Brennan et al. (2016) emphasized the importance of identifying high-risk medical
students and providing them with coping techniques without stigmatizing them. Henning
et al. (2011) suggested that interventions should be integrated into the curriculum to
promote resilience, good study habits, and optimize learning outcomes for students
(Henning et al., 2011). Having wellness programs incorporated into the required
curriculum may negate the psychological risk factors along with effects on academic
performance and promote long-term, positive quality of life (Brennan et al., 2016).
Although the literature reveals stress management has been beneficial for
reducing medical students’ stress levels, a standard conclusion across these voluntary
programs is that stress management should be required for all medical students or
integrated into the curriculum for greater effectiveness (Ayala et al., 2018; Henning et al.,
2011; Yusoff et al., 2013). As a means for stress prevention or active stress management,
medical schools could help students by embedding a stress management module into the
curriculum, primarily during the first year of training, as a required resource at a time
when students are seemingly the most stressed (Hathaisaard et al., 2022).
Required Stress Management Programs
Regardless of former researchers calling for required stress management for
medical students (Ayala et al., 2018; Henning et al., 2011; Yusoff et al., 2013), very few
studies have been conducted on required stress management programs. Dyrbye et al.

43
(2013) suggested that a comprehensive and rigorous approach be taken to justify the need
for wellness and support programs for medical students.
To help medical students better manage their stress while enrolled in medical
school, Kakoschke et al. (2021) conducted a 5-week intervention study designed to foster
behavior, attitudes, and competencies to help learn self-care strategies, enhance physical
health, understand the mind-body relationship, develop a holistic approach to healthcare
and medicine, and enhance performance on first-year undergraduate medical students.
The authors attributed the success of this program to the fact that it was integrated into
the core curriculum and required for all students (Kakoschke et al., 2021). After Kushner
et al. (2011) assessed the Behavior Change Plan outcomes in medical students, they
agreed that allowing students the opportunity to implement strategies to change their
behavior and improve personal health while enrolled in a designated required course
during the academic year had shown to be beneficial for students and successfully
incorporated into the medical school curriculum (Kushner et al., 2011).
The research showed that curricular changes are necessary to assist medical
students with managing their stress. Slavin et al. (2014) explored multiple medical
student wellness programs to understand the effects of preventive curricular changes for
improving well-being and found that curricular changes - including incorporating
required stress management training and learning communities that promote wellness -
proved to be effective for decreasing symptoms of depression and anxiety. Erogul et al.
(2014) agreed that interventions, specifically mindfulness-based stress reduction
programs, were found to be effective when embedded into the medical school curriculum,

44
but the researchers suggested that medical schools develop shortened versions of these
types of interventions to enhance and maintain student wellness and support professional
development in medical students. Slavin et al. (2014) added that medical schools should
routinely monitor students’ mental health and design interventions that are directly
applicable for the institution and their unique set of students instead of implementing a
one-size fits all model.
Tailoring stress management programs to fit the institution and student body so
that they integrate well into the curriculum is important. Polle and Gair (2021) conducted
a narrative review and found that multiple factors influence the effectiveness of the
program and often include things like hesitation to experience mindfulness and a general
lack of engagement, which can affect how well the students benefit from the program.
Furthermore, some medical students who have volunteered to participate in mindfulness-
based stress management programs believed those types of programs were beneficial and
should be integrated into the curriculum to assist all students, while other students felt
that integrating the program into the curriculum was counterproductive by occupying
students’ study and personal time (Dyrbye et al., 2017). To avoid incorporating a
counterproductive stress management program into the curriculum, Dyrbye et al. (2017)
suggested that schools review the attitudinal, engagement, and well-being measures of
their students before embedding a stress management program into the curriculum to
determine if participants would have experienced greater stress had they not been
required to participate in the program.

45
Research Methods and Designs From the Literature
Researchers have used multiple methods for measuring medical students’ stress
levels. Scales and questionnaires were found to be commonly used in the literature.
Commonly used instruments include the Depression, Anxiety and Stress Scale, PSS,
Satisfaction with Life Scale, General Self-Efficacy Scale, and the General Health
Questionnaire, all of which have been found to be good indicators of measuring self-
reported stress, depression, anxiety, quality of life and self-efficacy. Although these
instruments can be seen in various articles, the study designs in which the authors used
these resources vary greatly. While some studies were implemented using a qualitative or
mixed methodology, most research reviewed used a quantitative method. The range of
research designs found in the literature was greater than expected and include a small
number of longitudinal studies.
Qualitative Studies
Even though qualitative methodologies encompass the dynamics needed to
conceptualize the phenomenon, a review of the literature revealed that very few studies
have used qualitative methods for gathering data on medical students’ stress (Ravitch &
Carl, 2016). Many researchers have revealed several thematic elements related to medical
students’ stress. Identified themes could be categorized as curriculum-related and
personal. Curriculum-related thematic elements included exams, attendance, medical
responsibility, incomplete or missing medical resources, and unsupportive learning or
working environments (Polle & Gair, 2021; Daskivich et al., 2015). Whereas personal
themes affecting medical students’ stress levels included fear of failure, diet and exercise,

46
time management, and difficulty adjusting to change as major contributors to stress
(Daskivich et al., 2015; Kushner et al., 2011; Pohontsch et al., 2018). To explore the
thematic elements further, researchers have utilized a variety of research designs to delve
deeper into the phenomenon and identify potential solutions.
In a cross-sectional study, Dhandapani et al. (2022) used questionnaire-based
surveys to seek an understanding of how socio-demographic details and daily life factors
contributed to medical students’ stress. Results showed that students experienced
moderate to high stress levels as a result of the medical school curriculum, heavy
workload, exam grades, falling behind in the schedule and a vast curriculum that
continually changes throughout the semester (Dhandapani et al., 2022). Participants in
this study, 67%, indicated the need for their medical education curriculum to help
minimize stress. In another study, Pohontsch et al. (2018) used interviews to investigate
the perceived stressors in anticipation of implementing curricular changes. The
interviews were led by board-certified physicians as well as by a professor and
postdoctorate researcher, all using semi-structured interviews. By using interviews to
reveal the actual stressors medical students were experiencing, the researchers found that
the stressors were not specified by participant perceptions but were instead presented
within the medical school curriculum and setting (Pohontsch et al., 2018).
The qualitative approaches researchers have used for conducting studies on
medical students’ stress has differed over the years and results in different findings.
Radcliffe and Lester (2003) conducted a qualitative study on 5th-year medical students
using semi-structured interviews and found that the pressure of the workload was

47
reported as the most stressful aspect of medical education. Through semi-structured
interviews, students opened up and revealed that the transitional periods (undergrad to
medical school, preclinical training to clinical training, and clinical training to post-
graduate training) were identified as stressful to medical students and a lack of support
and resources from the administration added to students’ stress levels (Radcliffe &
Lester, 2003). Rather than using interviews, Jordan et al. (2020) used surveys and
questionnaires to explore the affects depression, burnout, and anxiety had on medical
students and found that simply being a medical student puts one at risk for experiencing
depression, anxiety, and burnout. Using a mixed-methods pretest and posttest design with
open-ended questionnaires and standardized scales to capture experiences and
satisfaction with a mindfulness-based stress reduction, Aherne et al. (2016) found that the
scheduling for a required stress management program was critical when embedding a
program into the curriculum.
When integrating stress management programs into the curriculum, the timing
and requirements of the program as an addition to what is already required should be
considered prior to making curricular changes. During a qualitative intervention study,
many first-year students deemed the program great but poorly executed due to poor
timing of the scheduled course, while the second-year students praised the benefits of the
program for helpfulness beyond the scheduled module and enjoyed the environment of
the session (Aherne et al., 2016). Herizchi et al. (2016) also found that group
participation was helpful for addressing mild to moderate stressors, not severe stressors.
The researchers noted that some students felt they needed more practice and training

48
while some students did not find stress management techniques effective (Herizchi et al.,
2016). To counteract this, researchers suggested that medical schools could undertake
preventive measures to minimize stress among their medical students (Jordan et al.,
2020), or develop courses for stress management during the different stages of medical
training (Herizchi et al., 2016).
Quantitative Studies
The quantitative methods that have been the most frequently used to explore
medical students’ stress levels have varied over the years. A common theme found in the
literature for capturing data related to medical students’ stress is the use of standardized
instruments for measuring perceived stress levels, depression, burnout, well-being, and
quality of life. Several recurring instruments have been identified throughout the studies
over the years. Based on the purpose of the study, a variety of surveys could be used. The
most commonly used scales found in the literature include the Depression, Anxiety and
Stress Scale, PSS, Satisfaction with Life Scale, General Self-Efficacy Scale, the World
Health Organization Quality of Life, Motivated Strategies for Learning Questionnaire,
and the General Health Questionnaire, all of which have been found to be good indicators
of measuring self-reported stress, depression, anxiety, quality of life and self-efficacy for
their respective studies. In more recent years, researchers seemed to expand on the study
designs to dig deeper into the phenomenon, incorporating experimental, longitudinal, and
observational studies to gain more insight on the effects of stress management on medical
students (Saleh et al., 2018; Seedhom et al., 2019; Slavin et al., 2014). The expanded and
experimental research designs have provided information and guidance on how medical

49
schools might choose to integrate stress management programs into their core curriculum
if deemed beneficial for their school and students.
To assess medical students’ stress levels, researchers have used a variety of
instruments and scales based on preference and study design to quantify data. Henning et
al. (2011) used anonymous questionnaires to assess motivation to learn, quality of life
and academic achievement and found that the scale instruments proved psychometric
validation in their study. Through the use of a variety of scales and instruments including
the Maslach Burnout Inventory, Primary Care Evaluation of Mental Disorders, Medical
Outcomes Study Short Form, Epworth Sleepiness Scale, and PSS, Dyrbye et al. (2013)
were able to identify 62 possible combinations of stress reported by medical students
with the most common occurrences being stress with burnout, exhaustion, high stress
levels, low quality of life and depressive symptoms. Likewise, Ling et al. (2016) showed
through the use of student responses to scale instruments that heavy study schedules and
insufficient support resources greatly impacted students’ stress and burnout levels. When
using a quantitative study design, Saleh et al. (2016) recommended that researchers
recognize the importance of incorporating positive variables in the study design for
preventing mental health issues in the student populations and to ensure the positive
variables are considered when creating mental health programs (Saleh et al., 2016).
To understand the prevalence of stress among Egyptian medical students,
Seedhom et al. (2019) conducted a cross-sectional study and found a significantly higher
percentage of stress levels in medical students throughout Egypt compared to nonmedical
students. Slavin et al. (2014) made several preventive curricular changes over a span of

50
five years in response to medical students’ stress responses in a longitudinal,
experimental research design. This approach included interventions to improve students’
mental health, implementing a pass/fail grading system, and allowing students the
opportunity to decide how they focus their studies, and it was found to be effective for
managing medical students’ well-being within their institution (Slavin et al., 2014). Saleh
et al. (2016) opted to conduct an exploratory study to understand how to best help college
students cope with stress and found that medical schools should try to incorporate
positive variables when creating and embedding mental health programs into the medical
school curriculum (Saleh et al., 2016).
Although the primary goal may be to develop and implement a long-lasting
effective stress management program for medical students, there are few longitudinal
studies that support the need for these programs or address the frequency of mental health
challenges among medical students. Zivin et al. (2009) conducted a longitudinal study
using a logistic regression analysis to better understand the factors related to mental
health and treatment and found that depression remained constant in participants when a
parallel study was designed and conducted after five years, suggesting that mental health
issues seemed to be related to more than transitional period adjustments (Zivin et al.,
2009). Also using an experimental design, Saleh et al. (2018) implemented an internet-
based stress management program to understand the effectiveness of cognitive-behavioral
therapy and ultimately found that that type of intervention program may have the ability
to reach many students due to the short format and ease of accessibility and a design
appeal targeted to students who do not seek professional help with managing their mental

51
health (Saleh et al., 2018). Nor and Smith (2019) argued in their longitudinal
correlational study that student personality and commitment were found to be the most
predictive variables for predicting medical students’ well-being and that it was not
necessarily the program design that made the most difference. It has been further
emphasized that the relationships between training attitudes and well-being are critical
factors when designing specific training programs (Nor & Smith, 2019).
Summary and Research Gap
The review of the literature included in Chapter 2 reveals that it is important to
continuously monitor medical students’ mental health since stress is a common
phenomenon seen in medical students (Norphun et al., 2020; Dyrbye et al., 2013; Goebert
et al., 2009; Saleh et al., 2017). Researchers have identified multiple factors that
contribute to medical students’ stress, including anxiety, burnout, quality of life,
employment status, and the demanding medical curriculum (Dhandapani et al., 2022;
Dyrbye et al., 2006; Henning et al., 2011). To assist students, some medical schools now
routinely monitor students for high-stress risks, and some have designed intervention
programs for students at risk (Hathaisaard et al., 2022; Loh et al., 2022; Slavin et al.,
2014). While research has shown voluntary stress management effective for medical
students, many researchers note that stress management programs have been beneficial
for reducing medical students’ stress levels and enhancing quality of life,
professionalism, and mental health by providing students with the skills they need to
manage and cope with stress, (Aherne et al., 2016; Dyrbye et al., 2013; Kushner et al.,
2011; Polle & Gair, 2021).

52
A variety of methods and study designs have been used to explore medical
students’ stress levels, the factors associated with this phenomenon and the means in
which medical schools can help their students manage their stress. Commonly seen
throughout the literature were quantitative designs using previously developed
instruments and scales to assess medical students’ stress levels, factors related to their
stress or effectiveness of a stress-management program. Regardless of design, however,
many researchers recommended additional research on the topic while also suggesting
that medical schools make stress management training a requirement for their medical
students by incorporating it into the curriculum (Brennan et al., 2016; Hathaisaard et al.,
2022; Pohontsch et al., 2018; Yang et al., 2018). Because stress is so common among
medical students, researchers suggest structuring student wellness programs or preventive
strategies to assist students with managing their stress (Dyrbye, et al., 2013). Researchers
also recommend additional research to determine how medical training can be structured
to reduce stress and identify or support students’ needs (Dyrbye et al., 2006). Henning et
al. (2011) study, noted that the medical school experience and a student’s well-being
interact with each other and that medical schools should consider a holistic approach
when designing the medical school curriculum to address the student’s mind, body, and
behavior as one unit. Hafferty and Franks (1994) noted that an effort to develop a
comprehensive curriculum should recognize the larger educational environment in which
the curriculum must flourish. In essence, the curriculum should not be a one size fits all
design. The studies shared in this review did not specify the type of medical program the
participants were enrolled in. However, to begin to consider the culture, it may be

53
important to differentiate two of the most common types of medical schools for students
in training to become U.S. board-certified physicians: allopathic (MD) medical schools
and osteopathic (DO) medical schools (Peters et al., 1999). One of the primary
differences between these types of study of medicine is that DO focuses on a whole-body
aspect, promoting well-being or a mind, body, and spirit approach to medicine (American
Osteopathic Association, 2019). While allopathic and osteopathic medical programs
share similarities in academia and board certification processes, the osteopathic medical
approach to treatment is a holistic process, which could suggest that stress management
could be approached in a different manner among this group of physicians in training.
With that said, specific research on how stress management programs affect DO students’
stress levels in relation to the osteopathic mindset has yet to be explored.
Since significant levels of stress are consistently reported by medical students
around the world, it is important for institutions to review their approach to addressing
this phenomenon (Dyrbye et al., 2013; Norphun et al., 2020). Studies show stress
management to be effective for reducing medical students’ stress levels, and voluntary
stress management programs have been consistently studied and shown effective for
reducing medical students’ stress levels (Dabrow et al., 2006; Greeson et al., 2015;
Henning et al., 2011). However, it is still unknown how participation in a stress
management module affects medical students’ stress levels, specifically DO students,
whose medical training includes a concept that takes a holistic approach to medicine.
A review of the literature confirms that medical students experience higher stress
levels and reveals that stress management has been helpful for reducing medical students’

54
stress levels (Dahlin et al., 2005; Ruzhenkova et al., 2018; Yusoff et al., 2013). Study
groups and peer-support programs have been identified as helpful coping strategies for
managing stress by allowing medical students to support each other during the pre-
clinical and clinical years of study (Abrams et al., 2022; Khine Myint Oo & Mohanan,
2019). There is also evidence that suggests that medical schools can do more to assist
their students by embedding stress management training into the medical school
curriculum (Hathaisaard et al., 2022; Slavin et al., 2014; Yang et al., 2018). Yet, it is still
unclear how participation in a stress management module would affect DO students’
stress levels, a facet of the phenomenon that has yet to be thoroughly explored. The gap
in the research is that there was little research published on DO students’ stress levels
when provided stress management resources, focusing on the first year of DO school.
Conclusion
In conclusion, a review of the literature revealed stress among medical students
was a common occurrence. Studies also show stress management as an effective tool for
coping with medical school stress (Dyrbye et al., 2017; Norphun et al., 2020; Yusoff et
al., 2013). A plethora of studies and a variety of research designs have shown that
medical students seem to respond well to stress management when participating both
voluntarily or involuntarily being required to complete stress management modules in
conjunction with the medical program (Aherne et al., 2016; Polle & Gair, 2021; Slavin et
al., 2014; Yang et al., 2018). Many researchers suggest medical schools require students
to participate in required stress management for longer retention of techniques (Brennan
et al., 2016; Pohontsch et al., 2018; Scholz et al., 2016). Given that Quick and Quick’s

55
(1984) theory of preventive stress management suggests that early recognition of stress
and implementing immediate measures to reduce and manage stress are beneficial and
Bandura’s (1977) self-efficacy theory suggests that coping mechanisms can alter and
maintain the power of an individual’s self-efficacy, one can recognize how participation
in required stress management training could be helpful for medical students.
However, to date, these studies seem to focus solely on traditional medical
students (MD programs) and do not include DO students or osteopathic programs. The
study focused on this growing population and the associated gap reflected in the
literature. In this research study, I explored the effect that participation in a stress
management module had on DO students’ stress levels as a preventive measure. This
research could help identify whether curricular enhancements could be considered
beneficial by incorporating a stress management course for managing DO students’ stress
levels.
In Chapter 3, I describe the research method and design that I used in the study to
better understand how participation in a stress management module affected DO
students’ stress levels. I also identify the research question and hypotheses that help guide
the study. I describe the study’s methodology addressing the target population, sampling
procedures, procedures for recruitment, and the procedures used for data collection. In
the following chapter I also describe the instruments and scales used in the study, detail
the operationalization of the study, identify the threats to validity and note the ethical
procedures taken to develop and execute a quality research study that focuses on the
effect participation in a stress management module has on DO students’ stress levels.

56
Chapter 3: Research Method
The purpose of the quasi-experimental study was to assess the effect of
participation in a 4-week stress management module on first-year DO students’ stress
levels. This chapter will detail the research design and rationale for the study, which
incorporates a quasi-experimental presurvey/postsurvey design. This design allows the
researcher to experiment without the use of randomization within the sample, a valuable
component in the design that adequately supports the study at the intended institution
(Harris et al., 2006). The research question and hypotheses also align with the study’s
intent to understand the effect participation in a stress management module has on first-
year DO students’ stress levels. I present the methodology of the study before identifying
the study’s population and sampling procedures. In support of the presurvey/postsurvey
design, the primary instrument was the PSS (see Cohen et al., 1983), which was
administered to participants before and after participating in the stress management
module. I used SPSS software, which is a quantitative analysis software developed for
collecting and assessing data, to manage and compute the data for the study.
This chapter also addresses several threats to validity within the study, which
includes the quasi-experimental design. Additionally, ethical procedures will be
demonstrated to ensure validity and protection of the participants. In addition to going
through Walden University’s Institutional Review Board (IRB), the study was also
subject to the institution’s IRB where the study’s data were retrieved.

57
Research Design and Rationale
This study’s variables included DO students’ stress levels as the dependent
variable and participation in the 4-week stress management module as the independent
variable. The quasi-experimental research design has been deemed useful when
conducting research that evaluates the effectiveness of a program (Gribbons & Herman,
1996). This design uses comparative data from observed outcome measures and is
specifically used when evaluating educational programs when random assignments to a
treatment group and control group are not feasible. The quasi-experimental design
typically tends to be deployed when assignment to the treatment is selected by
participants through self-selection or assigned by administrator selection (White &
Sabarwal, 2014). For purposes of this study, the research design did not have a control
group. Instead, I identified one group for use as both a baseline and comparison group
through outcome measurements from a set of responses to the presurvey scale and a set
of responses to the same scale in a postsurvey to understand three phases during the
study: observation before treatment (presurvey), introduction of the treatment
(intervention), and observation after treatment has been introduced (postsurvey). The PSS
was used to capture both the presurvey and postsurvey measurements. Using this design,
or O1 X O2, the differences between observations were used to estimate the effect size
of the treatment (Millsap & Maydeu-Olivares, 2009). A related-samples Wilcoxon signed
rank test was used to assess the difference between the presurvey and postsurvey results
from the one-group sample.

58
With a quasi-experimental design, observations are obtained from different time
periods, allowing the researcher to compare the effects of treatment (Millsap & Maydeu-
Olivares, 2009). The quasi-experimental pretest-posttest design, referenced as presurvey
and postsurvey in this study, has been deemed a simple design to implement with the
major disadvantage being that the difference in the pretest and posttest outcomes could be
associated with one specific treatment experience (Millsap & Maydeu-Olivares, 2009). It
would have been ideal to assess treatment over multiple points in time and with several
groups, but this method was not a feasible component for the study since the curriculum
is set in advance. It would be improper to add to the burden of stress that medical
students face when curricular changes are made throughout the year (Dhandapani et al.,
2022; Dyrbye, Power, et al., 2010). Incorporating the quasi-experimental
presurvey/postsurvey design in the study was sufficient to contribute to the literature by
adding research that advances knowledge on the effects of participation in a stress
management module on first-year DO students’ stress levels.
Methodology
Population
Being that the stress management module had to be completed while students
were actively enrolled in the program of study, all enrolled first-year DO students were
eligible to participate since they complete the program curriculum simultaneously. The
size of the population for the study was 188 students and only included the students who
matriculated with the Class of 2025 or students who were repeating their first year of the
DO program with the Class of 2025. The population could decrease if a student

59
withdraws from the DO program or is administratively dismissed for disciplinary or
academic reasons during the study. At no point during the study was the number of
participants from the target population expected to increase.
Sampling and Sampling Procedures
A control group was not feasible for this study due to the structure of the
program’s design, so all students enrolled in the first year of their DO program at the DO
school were asked to participate. Obtaining the census sample was explicitly gained from
the currently enrolled first-year DO students at the study site. All other students enrolled
in a program at the institution were excluded. The use of census sampling was effective
to use as it offered a large participant pool. Yet, it was ineffective as it excluded 75% of
students enrolled at the study site. The target population was invited to participate in the
study through email, and I used the institutional cohort group email to invite the sample.
To capture the required sample size needed for the study and statistical analysis, I
used the G*Power calculator to determine the effect size, alpha level, and power level of
the sample (Erdfelder et al., 1996). Using the G*Power tool to calculate the power of
analysis, the required sample size for the study would be 64 participants, using the same
sample group of students for the presurvey and postsurvey. For a medium effect size
(Cohen’s d = 0.50), an alpha level set at 0.05 and power set to .80 to observe an effect if
one should occur would also be needed. A power of analysis is needed to validate the
study and to avoid Type I and Type II error (Jones et al., 2003).
Although the stress management module was incorporated while students were
enrolled in a course that all DO students must complete for program requirements, the

60
majority of the students did not wish to participate in the study. Only 30 students
participated in the study and completed the PSS presurvey, while about half (n = 11)
completed the postsurvey assessment.
Procedures for Recruitment, Participation, and Data Collection
Recruitment
As the primary researcher, I sent the study invitation and the informed consent
form to all first-year DO students enrolled in a Foundations course through their
institutional email address. The individual email addresses were obtained by cohort group
in the study site’s email address book. Students were asked to respond to the email if they
were interested in participating in the study, which garnered 12 participants. After the
initial 4-week recruitment period and five reminders to the target population, the study
site’s IRB recommended that I send a variation of the recruitment invitation to the entire
class and extend the recruitment period until more students indicated interest. The
variation to the invitation included emailing the target population a Microsoft Forms link
with the opening page being the actual invitation to participate in the study as well as the
informed consent form. After reading the invitation, students could elect to agree to
participate in the study or decline participation. If students agreed to participate, they
were immediately taken to the PSS presurvey, which I had built into the next page of the
Microsoft Form. If the students declined to participate, they were taken to the end of the
survey and thanked for their response.

61
Participation
If a student enrolled in the Foundations course was interested in participating in
the study based on the study invitation, I asked them to complete the PSS which was used
to capture general self-reported stress at the baseline level before beginning the stress
management module. The Foundations course is a course that covers topics on how to
become a successful physician. Lectures and exercises in this course frequently cover
topics that reference the importance of well-being, nutrition, physical exercise, and stress
management, making it the ideal course in which to place the stress management module,
as it could enhance the structure of the course. Working closely with the Foundations
course director while students completed the course and the stress management module, I
communicated the study overview, requirements, stress management techniques, and the
pre- and postsurvey instruments through my institutional email account for the
Foundations course director to pass on to participants.
While I waited for responses to the PSS and with the associate dean of student
services’ approval, I used my access to the student database to retrieve a roster of names
with institutional email addresses, gender, and date of birth of all the first-year students
enrolled in the Foundations course at the study site. I used this roster to keep track of the
presurvey responses based on the email address of each student who submitted a response
on the Microsoft Form, as the Form was built to share the individual email address of the
PSS respondent with the Form creator. Additionally, I asked the students to complete the
PSS after the 4-week module ended to capture the comparison data.
Data Collection

62
As the primary researcher, I collected the PSS data while students were actively
enrolled in the Foundations course. I deidentified the responses by removing the email
address and randomly assigned a special numeric code to students. Having the
spreadsheet of the special numbers, I was able to match participant presurvey and
postsurvey responses and identify missing responses. I then compared the responses to
determine the effect that participation in the 4-week module had on DO students’ stress
levels. Since personal demographics may contribute to participant responses, participant
demographics – age and sex – were collected separately before participants submitted
their presurvey and postsurvey responses to the PSS. Data were stored securely in an
excel spreadsheet on my personal password-protected computer. At the end of the PSS
postsurvey, I thanked the participants through a customized thank you page. The message
also indicated that the results of the study would be shared once the study had been
finalized.
Instrumentation and Operationalization of Constructs
Cohen et al. (1983) developed the PSS, which is a 14-item Likert-scale survey
that is used to assess an individual’s current perceived stress level (Cohen et al., 1983).
The PSS asks individuals to report their experiences of stress and stress response within
the last month on a scale of zero to four with 0 = never, 1 = almost never, 2 = sometimes,
3 = fairly often, and 4 = very often (see Appendix A). Each pre- and postsurvey was
completed electronically and took no more than 15 minutes to complete. This instrument
has been identified as a helpful tool for measuring how one perceives daily life situations
as stressful in a variety of individuals with multiple variables applied, including age,

63
gender, race, and economic status (Cohen & Janicki-Deverts, 2012). Furthermore, the
developers’ consent to use the instrument has been openly granted for student and
nonprofit organizations use and is included in Appendix B.
The PSS has also been shown as a reliable and valid tool for assessing perceived
stress and shown to exhibit construct validity (Cohen & Williamson, 1988; Hewitt et al.,
1992; Warttig et al., 2013), making it a valuable resource to use in this study. When
Cohen and Williamson (1988) tested the validity of the scale relative to life events, the
researchers found that users with higher perceived stress scores were more likely to
display psychological symptoms of stress. Warttig et al. (2013) used a shortened version
of the PSS to understand the relationship between stress scores and sociodemographic
factors among a sample of over 1,550 English participants. Using Cronbach’s alpha,
Warttig et al. found that the shortened version of the scale was a reliable and valid tool
for accessing stress perceptions among international participants (α = 0.77). Similarly,
Martínez and Rábago (2019) found the PSS to be a valid tool when used to assess
perceived stress among 400 Cuban medical students. Cronbach’s alpha (0.84) revealed
scale reliability, allowing the researchers to conclude the PSS as a reliable instrument for
identifying perceived stress among medical students and some of the factors that
influence their stress (Martínez & Rábago, 2019). Once a participant completes the scale,
all numbers are added together to indicate the person’s perceived stress. Due to the
positivity of Questions 4, 5, 6, 7, 9, 10, and 13 in the scale, the responses are scored in
reverse order based on the instrument calculation instructions (see Cohen et al., 1983).

64
Intervention
The stress management module was adapted from Demarzo et al.’s (2017)
controlled study on the efficacy of an 8-week mindfulness-based intervention and a 4-
week mindfulness-based intervention. Using the 4-week mindfulness intervention as
guidance, the stress management module for this study encompassed a variety of stress
management techniques and resources for students to incorporate into their daily
schedules. These techniques range from quick stretches, breathing exercises, reading
materials on managing stress and mindfulness exercises (Demarzo et al., 2017). The
stress management module was in place for the allotted 4-week timeframe for students to
use on a weekly basis as the materials were emailed to the participants’ institutional email
addresses.
Using the Demarzo et al.’s (2017) 4-week mindfulness intervention, the stress
management module for this study encompassed a variety of stress management
techniques and resources for students to incorporate into their daily schedules. I
implemented the stress management module by sending each week’s module materials
(see Appendix C) to the Foundations course director who then shared the module with the
list of students who agreed to participate in the study. The Foundations course director
remained cautious when communicating with the participants understanding that they
were already stressed while studying for final exams for their systems-based courses. As
a precaution, the course director sent the reminders to participate in the study, which
included the link to the PSS, and complete the presurvey after the participants had
completed their second final exam for the semester.

65
The PSS served as the pre- and postsurvey instruments for the study. Students
received the link to complete study instruments in their institutional email account to self-
report stress and well-being before the module began and again after the module ended.
Participants were asked to complete the PSS as a presurvey before the first week of
implementing the module. The same outcome measure was administered following
completion of the 4-week module as a postsurvey. Weekly reminders were sent to the
participants to encourage postsurvey submissions. I planned the entire study to last 11
weeks of the 21-week Foundations course (4 weeks for recruitment, 2 weeks for the
presurvey, 4 weeks for the stress management module, and 1 week for the postsurvey).
Because I extended the recruitment period, the entire study ran for the full 21 weeks of
the course.
The stress management module information was originally planned to be included
in the course syllabus as no grade was assigned to students for completing the module.
Instead, the module was shared while students were participating in the Foundations
course when topics of stress management, mental health, or well-being were being
discussed. The stress management module included presentations, literature, and
exercises on how to effectively manage stress and were encouraged by the course director
to allow seamless incorporation of the module while students completed the course. The
module included self-guided stress management exercises to allow students to complete
the exercises as their schedules allowed.

66
Operationalization of Variables
The DO students’ stress levels, the dependent variable in this study, refer to the
level of stress participants were self-assessing at the time of completing the PSS
presurvey and postsurvey. Participation in the 4-week stress management module, the
independent variable, refers to the 4 weeks of stress management exercises that
participants completed before submitting responses to the PSS postsurvey. In the PSS,
participants self-assessed their stress levels over the last 30 days and provided scale
responses for all 14 questions in PSS. The scale from the PSS ranged from 0 to 4 with 0 =
never, 1 = almost never, 2 = sometimes, 3 = fairly often, and 4 = very often. Due to the
positivity of Questions 4, 5, 6, 7, 9, 10, and 13, the responses for these questions were
reverse coded based on the instrument calculation instructions, with 0 = very often, 1 =
fairly often, 2 = sometimes, 3 = almost never, and 4 = never (see Cohen et al., 1983). All
variables were measures as interval measures, and higher cumulative total scores on the
PSS indicated higher levels of perceived stress (Cohen et al., 1983).
Data Analysis Plan
I used the IBM SPSS Statistics software (Version: 28.0.1.0) provided through
Walden University to analyze the data in this quasi-experimental study. I cleaned the pre-
and postsurvey data through SPSS before analysis to ensure the postsurvey results were
appropriately matched to each student’s respective presurvey results prior to analysis. To
do this, I merged both sets of responses, ensuring a response had been provided for the
participant’s randomly assigned number and made sure the unanswered responses did not
include a “0” as a response since that was one of the options. I then went back to ensure

67
all the questions that needed to be reverse coded were appropriately reflected. This data-
cleaning process also revealed missing responses that could potentially skew the results.
Missing responses were removed from the sample, and the occurrence was noted in the
data analysis section.
RQ: What is the difference in first-year DO students’ stress levels as measured by
the PSS before and after they participated in a 4-week stress management module?
H0: There is no difference in first-year DO students’ stress levels as measured by
the PSS before and after participating in a 4-week stress management module.
Ha: There is a difference in first-year DO students’ stress levels as measured by
the PSS before and after participating in a 4-week stress management module.
Panchu et al. (2016) computed data using SPSS software to analyze medical
students’ data using t tests and found that most medical students experience academic
stress (p < 0.01) and that administration in charge of curriculum design should take this
finding into account. With support for using SPSS software as a quantitative analytic
software, I planned to use a paired t-test analysis to compare pre- and postsurvey data of
DO students’ self-reported stress to answer the research question. With a paired t-test
analysis, specific assumptions must be met for the researcher to confirm a valid result
(McCrum-Gardner, 2008). The four assumptions for the paired t-test analysis are (a) the
dependent variable should be numeric as either an interval or ratio, (b) the independent
variable should be comprised of two related groups, (c) the data should not contain
significant outliers, and (d) there should be normal distribution between the two groups
(Pandey, 2015). I determined the first two stated assumptions to be met prior to the data

68
collection. Although not anticipated because of the setting and nature of the intervention,
I did not know if there were any outliers or distribution differences until after testing the
sample in SPSS. I will further discuss the assumption testing and the use of the related-
samples Wilcoxon signed rank test, instead of the paired t-test in Chapter 4.
Comparing the median values from the presurvey to the median values from the
postsurvey determined whether statistical significance is seen between the two groups
using the related-samples Wilcoxon signed rank test. Statistical significance was defined
at p < 0.05, resulting in rejection of the null hypothesis for values below the threshold.
Because Cronbach’s alpha is commonly used in medical education research to measure
the reliability of a scale and to measure error variance within a test (Tavakol & Dennick,
2011), I used Cronbach’s alpha to test the samples’ internal reliability and verify that I
was measuring the same traits on the same scale. Descriptive statistics were used at each
stage during the analysis to clearly show any changes in participant data results, the
standard error of mean, and the confidence interval. The visual statistics were also shared
to clearly show the unexpected changes that occurred during the data collection and
analysis stages.
Threats to Validity
One of the major threats to validity is the research design, itself. For one, a quasi-
experimental design only consists of administering outcome measures to the program
group and comparison (Gribbons & Herman, 1996). For this reason, the quasi-
experimental design is considered ambiguous because it contains all the features of an
experimental design without the use of random assignment (Millsap & Maydeu-Olivares,

69
2009). Additionally, this design is limited to the range of evaluation for purposes of the
program. Because randomization is not feasible for the study, it is understood that the
approach is unique and unstandardized (Gribbons & Herman, 1996).
Another unique and possibly compromising feature of this study is that it
encompassed solely self-reported data, subjecting it to response bias. It also included a
relatively small sample size of 30 presurvey and 11 postsurvey participants from one
location. Additionally, only one statistical analysis - a related-samples Wilcoxon signed
rank test – was used for the study, extending the threats to validity further. Given the
multiple threats, statistical conclusion validity played an important role in analyzing and
presenting the data to ensure the correct conclusions were made. Since personal
demographics, such as age category and sex, may also play a role in participant
responses, they were, therefore, captured to help support results. A reliability test, such as
a correlation test, was also used to justify the validity of the results. Because the sample
size is small and the timeframe between each survey was relatively short with the same
group of respondents, a test-retest reliability was used to document reliability
measurements in the scores (see Litwin, 1995). Ultimately, this study was focused
primarily on understanding how participation in stress management modules affects DO
students’ stress levels as a whole to determine if it would be beneficial to implement a
curricular change that would help students manage their stress as they progress through
the DO school program.

70
Ethical Procedures
Agreements to gain access to the institution’s participants were collected after the
successful oral defense of the proposal. These agreements included two separate
applications: one to Walden University’s IRB (02-01-22-0654581) and another
application to the DO school’s IRB (HS220105-E), both of which required written
approval before moving forward with the study. The study site is the IRB of record for all
data collection. I received a verbal agreement to conduct the study at the site from the
associate dean of student services while waiting for IRB approval. As a courtesy while in
the IRB application stage, I discussed the study with the assistant dean of academic &
career support as well as the Foundations course directors so they could have awareness
of the intervention. Considerations about concerns raised by the faculty were noted and
addressed at that time. To protect the integrity of the study, I deidentified participant
responses by coding presurvey and postsurvey documents with a randomized numbering
system assigned to each student at the beginning of the study and managed on a
password-protected Excel spreadsheet. A written summary of the data results was shared
with the research committee and academic support representatives once finalized before
being shared with the participants. Data results may also be shared with the curriculum
committee and administration for use during strategic and curriculum planning.
Other ethical concerns included invited participants who did not complete the
surveys. There were also a couple of students who withdrew from the program before
having the opportunity to complete the stress management module and submit the
postsurvey. For the students who submitted one or both surveys for the study, I

71
referenced the deidentified randomized coded spreadsheet to remove any missing
responses from the sample. I maintained a record of those who did not submit a
postsurvey response to report in the final study. Additionally, the study involved
incorporating a stress management module while students were actively enrolled in the
DO program. The IRB approvals and consent for the study were available for all students
participating in the study’s module if they wanted to view the documents.
Another major ethical concern was that of conducting the study in my workplace.
My current involvement with curriculum processes, instruction, and student engagement
related to these matters is non-existent. There were no conflicts of interest or power
differentials between me as a researcher and the students as participants. However, there
may be a slight concern regarding response bias given the structure of the study being
released by an administrator to students. I as the researcher, however, did not guide
participants through the modules and only shared the materials related to the study as a
means of minimizing response bias.
Additionally, participant responses were deidentified. Each participant was
randomly assigned a number at the beginning of the study. This number was the only
identifying factor for matching presurvey and postsurvey responses and served as a
mechanism for tracking completed responses. Participant responses to the instruments
and scales remained confidential and voluntary to optimize outcome measures for the
student. I stored the responses securely in an Excel spreadsheet on my personal
password-protected computer to which no one had access to the device. The datasheet

72
was also password-protected and encrypted as an additional security layer should the
device or its contents be compromised.
I also maintained a backup of the password-protected datasheet on a personal
secure and encrypted USB flash drive used solely for the purpose of this study. Any
printed data were stored in a secure locked filing cabinet to which only I had the key. The
collected data will remain on my personal password-protected computer, on an encrypted
USB flash drive, and in the locked filing cabinet until the data destruction date. Data will
remain securely stored at the conclusion of the study, and I will personally delete the data
from the computer and USB flash drive at the end of the data retention period. I will also
shred any printed data stored in the locked filing cabinet at the end of the data retention
period. The process for data storage and destruction was shared with all study participants
during the debrief at the conclusion of data collection.
Summary
This quantitative quasi-experimental study was conducted to assess the effect
participation in a 4-week stress management module has on first-year DO students’ stress
levels. Stress management courses have been shown to be an effective tool for managing
traditional medical students’ stress levels (Aherne et al., 2016; Dyrbye et al., 2017; Polle
& Gair, 2021; Scholz et al., 2016; Slavin et al., 2014). Little has been published regarding
the effects of DO students’ participation in stress management modules. Using the pre-
existing PSS, the goal of the quasi-experimental study was to evaluate the effect that
participation in a stress management module on first-year DO students’ stress levels
through a presurvey/postsurvey research design and a paired t-test analysis to compare

73
presurvey and postsurvey data. Statistical significance was defined at p < 0.05, resulting
in rejection of the null hypothesis for values above the threshold.
The fact that the module was incorporated while students were enrolled in a
Foundations course that all students were required to complete at the same time did not
offer the opportunity to randomize students into a treatment group and a control group,
resulting in the quasi-experimental design. One of the major threats to validity using this
research design was the structure of the design, as it involves controlling outcome
measures in the program group (Gribbons & Herman, 1996). Another threat was that the
design was tailored to a specified program, which compromised the generalizability of
the study. The proper protocol was followed to gain access to the institution’s participants
and to conduct the study. A written summary of the results was shared with the research
committee, academic support representatives, and participants at the end of the study and
may also be shared with administration for use during strategic and curriculum summit
planning for review and modification of the curriculum, should the results reveal a
positive effect on DO students’ stress levels. Careful consideration and processes were
taken to address the ethical concerns associated with the study. Even with a variety of
threats to validity and ethical concerns, the study design was still deemed the most
appropriate for collecting data and understanding the effect participation in a stress
management module has on medical students’ stress levels.
In the next chapter, I will discuss the data collection process and report any
changes that occurred during the data collection stage that differed from the planning
stages as detailed in Chapter 3. I will also report the results of the study, including the

74
statistical analysis findings, confidence intervals, and effect sizes. In addition to these
details, descriptive statistics will also be provided to illustrate the effect participation in a
stress management module had on DO students’ stress levels.

75
Chapter 4: Results
The purpose of the quasi-experimental study was to assess the effect of
participation in a 4-week stress management module on first-year DO students’ stress
levels. One research question had been developed for the study:
RQ: What is the difference in first-year DO students’ stress levels as measured by
the PSS before and after they participated in a 4-week stress management module?
H0: There is no difference in first-year DO students’ stress levels as measured by
the PSS before and after participating in a 4-week stress management module.
Ha: There is a difference in first-year DO students’ stress levels as measured by
the PSS before and after participating in a 4-week stress management module.
In this chapter, I discuss the data collection process along with the data collection
challenges I experienced during the process. I also report the data from the study at both
the presurvey stage and postsurvey stage before transitioning into the analysis of the
results, including the statistical analysis findings, confidence intervals, and effect sizes. In
addition to these details, I provide descriptive statistics to illustrate the effect
participation in the 4-week stress management module had on DO students’ stress levels.
Data Collection
I received IRB approval (HS220105-E) from the study site on January 11, 2022,
followed by Walden University’s IRB approval (02-01-22-0654581) on February 1,
2022. The study site is the IRB of record for all data collection. Having all necessary
approvals in place, I downloaded a roster of names with institutional email addresses,
gender, and date of birth of all the first-year students enrolled in the Foundations course

76
at the study site. I had previously received verbal approval from the associate dean of
student services to obtain and use the roster for my study as long as the information
would be deidentified prior to being published in the study. As I am the registrar at the
study site, I was able to download this information and worked to remove the information
that was not needed for the study, maintaining a separate list of names and email
addresses for the students enrolled in the first-year Foundations course during Spring
2022.
I then blind copied all the students on the roster in a recruitment email from my
workplace email account. The recruitment email included the study invitation and
consent form to all the students enrolled in the course as of Monday, February 7, 2022. I
created an action rule for all recruitment and consent responses to automatically move to
a “Dissertation Responses” folder that I created in my workplace Outlook inbox so I
could automatically filter my work emails from the dissertation response emails and
forward the dissertation responses to my Walden email account if necessary. I sent a
recruitment reminder email on the evening of Friday, February 11, 2022, after the
students completed a final exam. I removed the students who had already consented to
participate in the study from the email chain. The following week included two more
reminders on Wednesday and Friday. With a low response rate of 6% at the end of the
recruitment period, I shared the number of responses I had received with the Foundations
course director and worked closely with the director to encourage students to consider
participating in the study. Rather than recruiting participants for 2 weeks, the recruitment
period lasted 10 weeks, receiving only 30 participants for a 16% response rate. After

77
discussing the numbers again with the course director and study site’s IRB, it was
determined that the low response rate was due to timing in the semester and to move
forward with the 30 participants.
Data Collection Discrepancies
After consulting with the course director and study site’s IRB for 2 weeks, I
decided to modify the recruitment approach to make it easier for students to consent to
participation, which was approved by the IRB of record on March 29, 2022. I
restructured the presurvey from Qualtrics to Microsoft Forms so the participants could
feel more comfortable using a survey format that they had already seen multiple times
before from the study site (see Appendix A). I also developed an easier way for the
participants to consent with the click of a button by building the invitation into a cover
page in Microsoft Forms that advanced to the PSS if there was consent. With this change,
I could no longer assign a random number to participants for matching the presurvey
response to the postsurvey response and had to collect names and email addresses to
match the responses. I shared that all responses would remain confidential and ultimately
deleted names from the raw data file I received to allow for greater confidentiality and
only referenced email addresses to match responses. Because of the changes to the
recruitment process, working around the students’ final exam schedules, Spring Break,
and other events in the semester, the recruitment period was extended from the planned 2
weeks to 10 weeks. Although the recruitment period was longer than originally planned,
the extended amount of time and modifications to the study’s recruitment and consent
during this timeframe resulted in a larger number of participants who completed the

78
presurvey and were forwarded the module materials. For reference, Table 1 outlines the
timeline of the study.
Table 1
Timeline
Study event
Duration of weeks
Dates
Participant recruitment
10
February 7, 2022 – April 18, 2022*
PSS Presurvey
1
April 11, 2022 – April 19, 2022**
Module 1: The raisin exercise
1
April 18, 2022 – April 24, 2022
Module 2: Breathing exercise
1
April 25, 2022 – May 1, 2022
Module 3: Body scan exercise
1
May 2, 2022 – May 8, 2022
Module 4: Walking meditation
1
May 9, 2022 – May 15, 2022
PSS Postsurvey
2
May 16, 2022 – May 29, 2022***
Note. Table 1 shows the timeline of the study from start to finish.
a Course director sent a final reminder the first week of the module and gained additional
participants.
b Delayed sending the PSS presurvey due to final exam schedule.
c Due to delays, the PSS postsurvey was scheduled to close on the same day the
Foundations course ended.
d All changes to recruitment procedures and timelines were discussed with both the study
site’s IRB and Walden’s IRB for approval prior to moving forward.
For the postsurvey, because I still wanted to capture any portion of the module
completed, the preliminary questions asked the participant to indicate the number of
weeks in the stress management module that were completed and also asked the
respondent to indicate which weeks they completed (see Appendix D). The structure of
the survey was formatted to allow the respondent to move forward with completing the
postsurvey questions if they had completed at least 1 week of the module. If the
participant indicated that they did not participate in any of the weekly module exercises,
they were not given the option to view the postsurvey. These participants were
automatically moved to the end of the form and thanked for their participation.

79
Data Collection Characteristics
At baseline before completing the PSS presurvey, 32 first-year DO students
agreed to participate in the study. There were 13 male students and 19 female students
who agreed to participate in the study. However, two of the female students did not meet
the eligibility requirements. The two ineligible students’ responses were excluded from
the presurvey results, bringing the total number of female participants to 17. Thus, a total
of 30 first-year DO students completed the PSS presurvey. Due to timing in the semester,
14 students responded to the invitation to complete the postsurvey. Only 11 students
completed the PSS postsurvey. Three participants - one female and two males - indicated
that they did not participate in any of the weekly modules and were not eligible to view
the postsurvey. A total of 11 participants - four male and seven female students - made up
the postsurvey sample. All participants were above the age of 23.
Intervention Fidelity
For purposes of this study, a 4-week stress management module was shared with
students while they were enrolled in a required Foundations course (see Appendix C).
The intervention ran 4 weeks during the end of the Spring term. I worked closely with the
course director and shared the study overview, requirements, stress management
techniques and the pre- and postsurvey instruments through my institutional email
account with the Foundations course director who then forwarded the information to the
students’ institutional email addresses. The PSS served as the pre- and postsurvey
instruments for the study. The Foundations course director distributed the presurvey links
to all first-year students enrolled in the course to encourage participation after my five

80
attempts to recruit a larger sample had been exhausted. The Foundations course director
also sent the links to the stress management module and postsurvey to the participants’
email addresses to determine participants’ perceived stress levels after the intervention.
Participants were encouraged to submit their perceived stress presurvey responses before
the first week of implementing the module and were also asked to submit their postsurvey
responses within 2 weeks after the stress management module had ended.
The 4-week stress management module for this study was taken from Demarzo et
al.’s (2017) controlled study on the efficacy of 8-week and 4-week mindfulness-based
interventions. Using only the 4-week session as guidance, the stress management module
encompassed a variety of stress management techniques and resources for students to
incorporate into their daily schedules. These techniques included quick stretches,
breathing exercises, reading materials on managing stress, and mindfulness exercises
(Demarzo et al., 2017). The stress management module was in place for the allotted 4-
week timeframe for students to use on a weekly basis as the materials are shared. The
purpose of the module was to understand if a short 4-week module has any effect on
managing or helping students’ stress levels while enrolled in a DO program that teaches
students to focus on holistic care for optimal well-being.
The module was administered as originally planned with no adverse events
reported. The only implementation challenge was the recruitment delay for student
participation, which delayed implementation of the module by several weeks. Otherwise,
the module was implemented as anticipated for 4 full weeks with the participants

81
submitting their responses to the postsurvey within 2 weeks of the stress management
module’s ending.
Results
The results from the study are categorized into three parts – presurvey results,
postsurvey results, and inferential statistics. The presurvey results reveal the data
collected at baseline before the 4-week stress management module was implemented. The
postsurvey results share data captured after the stress management module was
completed. In the inferential statistics section, I compare the postsurvey results to the
presurvey results using the related-samples Wilcoxon signed rank test. All sections
include an overview of the captured data along with descriptive statistics for reader
comprehension.
Presurvey Results
Changing the consent process allowed me to collect data from a larger sample, the
188 students enrolled. Since all students enrolled in their first year of studies at the study
site were invited to participate, I sent several study invitation emails to the Class of 2025
email group in a blind copy email. After exhausting the extended recruitment period at 4
weeks, the study invitation emails were sent by the Foundations course director until it
was time to begin the module. Ultimately, a total of 32 students from the email group
consented to participate in the study, with 13 males and 19 females all at least 23 years of
age or older completing the presurvey. While reviewing the presurvey data, I noticed that
two of the female participants who were not currently enrolled in the program responded
to the presurvey. Current enrollment in the program was one of the primary inclusion

82
criteria for the study, so I omitted those two responses bringing my total sample to 30
participants, a 16% response rate. The majority of respondents (80%) were between 23
and 27 years of age. Over 16% of respondents were between the ages of 28 and 32 while
over 3% were over the age of 40. Table 2 shows the demographic characteristics of the
sample of participants who completed the presurvey by gender and age. The participants
included 13 male DO students and 17 female DO students, and all participants were over
the age of 23.
Table 2
Demographic Characteristics (N = 30) by Age and Gender
Demographic characteristic
N
%
Gender
Male
13
43.33%
Female
17
56.67%
Age
18-22
0
0%
23-27
24
80%
28-32
5
16.67%
33-37
0
0%
38-42
0
0%
43-47
1
3.33%
The presurvey results revealed that all of the respondents reported feeling stressed
to some degree within the past 30 days. Over half of the participants reported feeling
stressed or nervous over the past month very often (59.4%), 25% reported the feeling
fairly often, 14% reported feeling stressed sometimes, and only 6% reported experiencing
the feeling as almost never. Additionally, a large majority of participants (75%) reported
feeling they were effectively coping with important changes in their life while only 25%
reported feeling like this almost never. Then when asked if they felt they could not cope

83
with all the things they had to do, half of the respondents indicated they felt this way
almost never (34%) or never (15%) while the other half reported feeling this way
sometimes (28%) and often (31%). When asked about thinking about the things they have
to accomplish in the future, about 97% responded to thinking about this often. Ultimately,
the presurvey results revealed that most of the participants experienced some type of
anger, stress, apprehension, or anxiety the month prior. Figure 1 and Figure 2 represent
all the presurvey results.
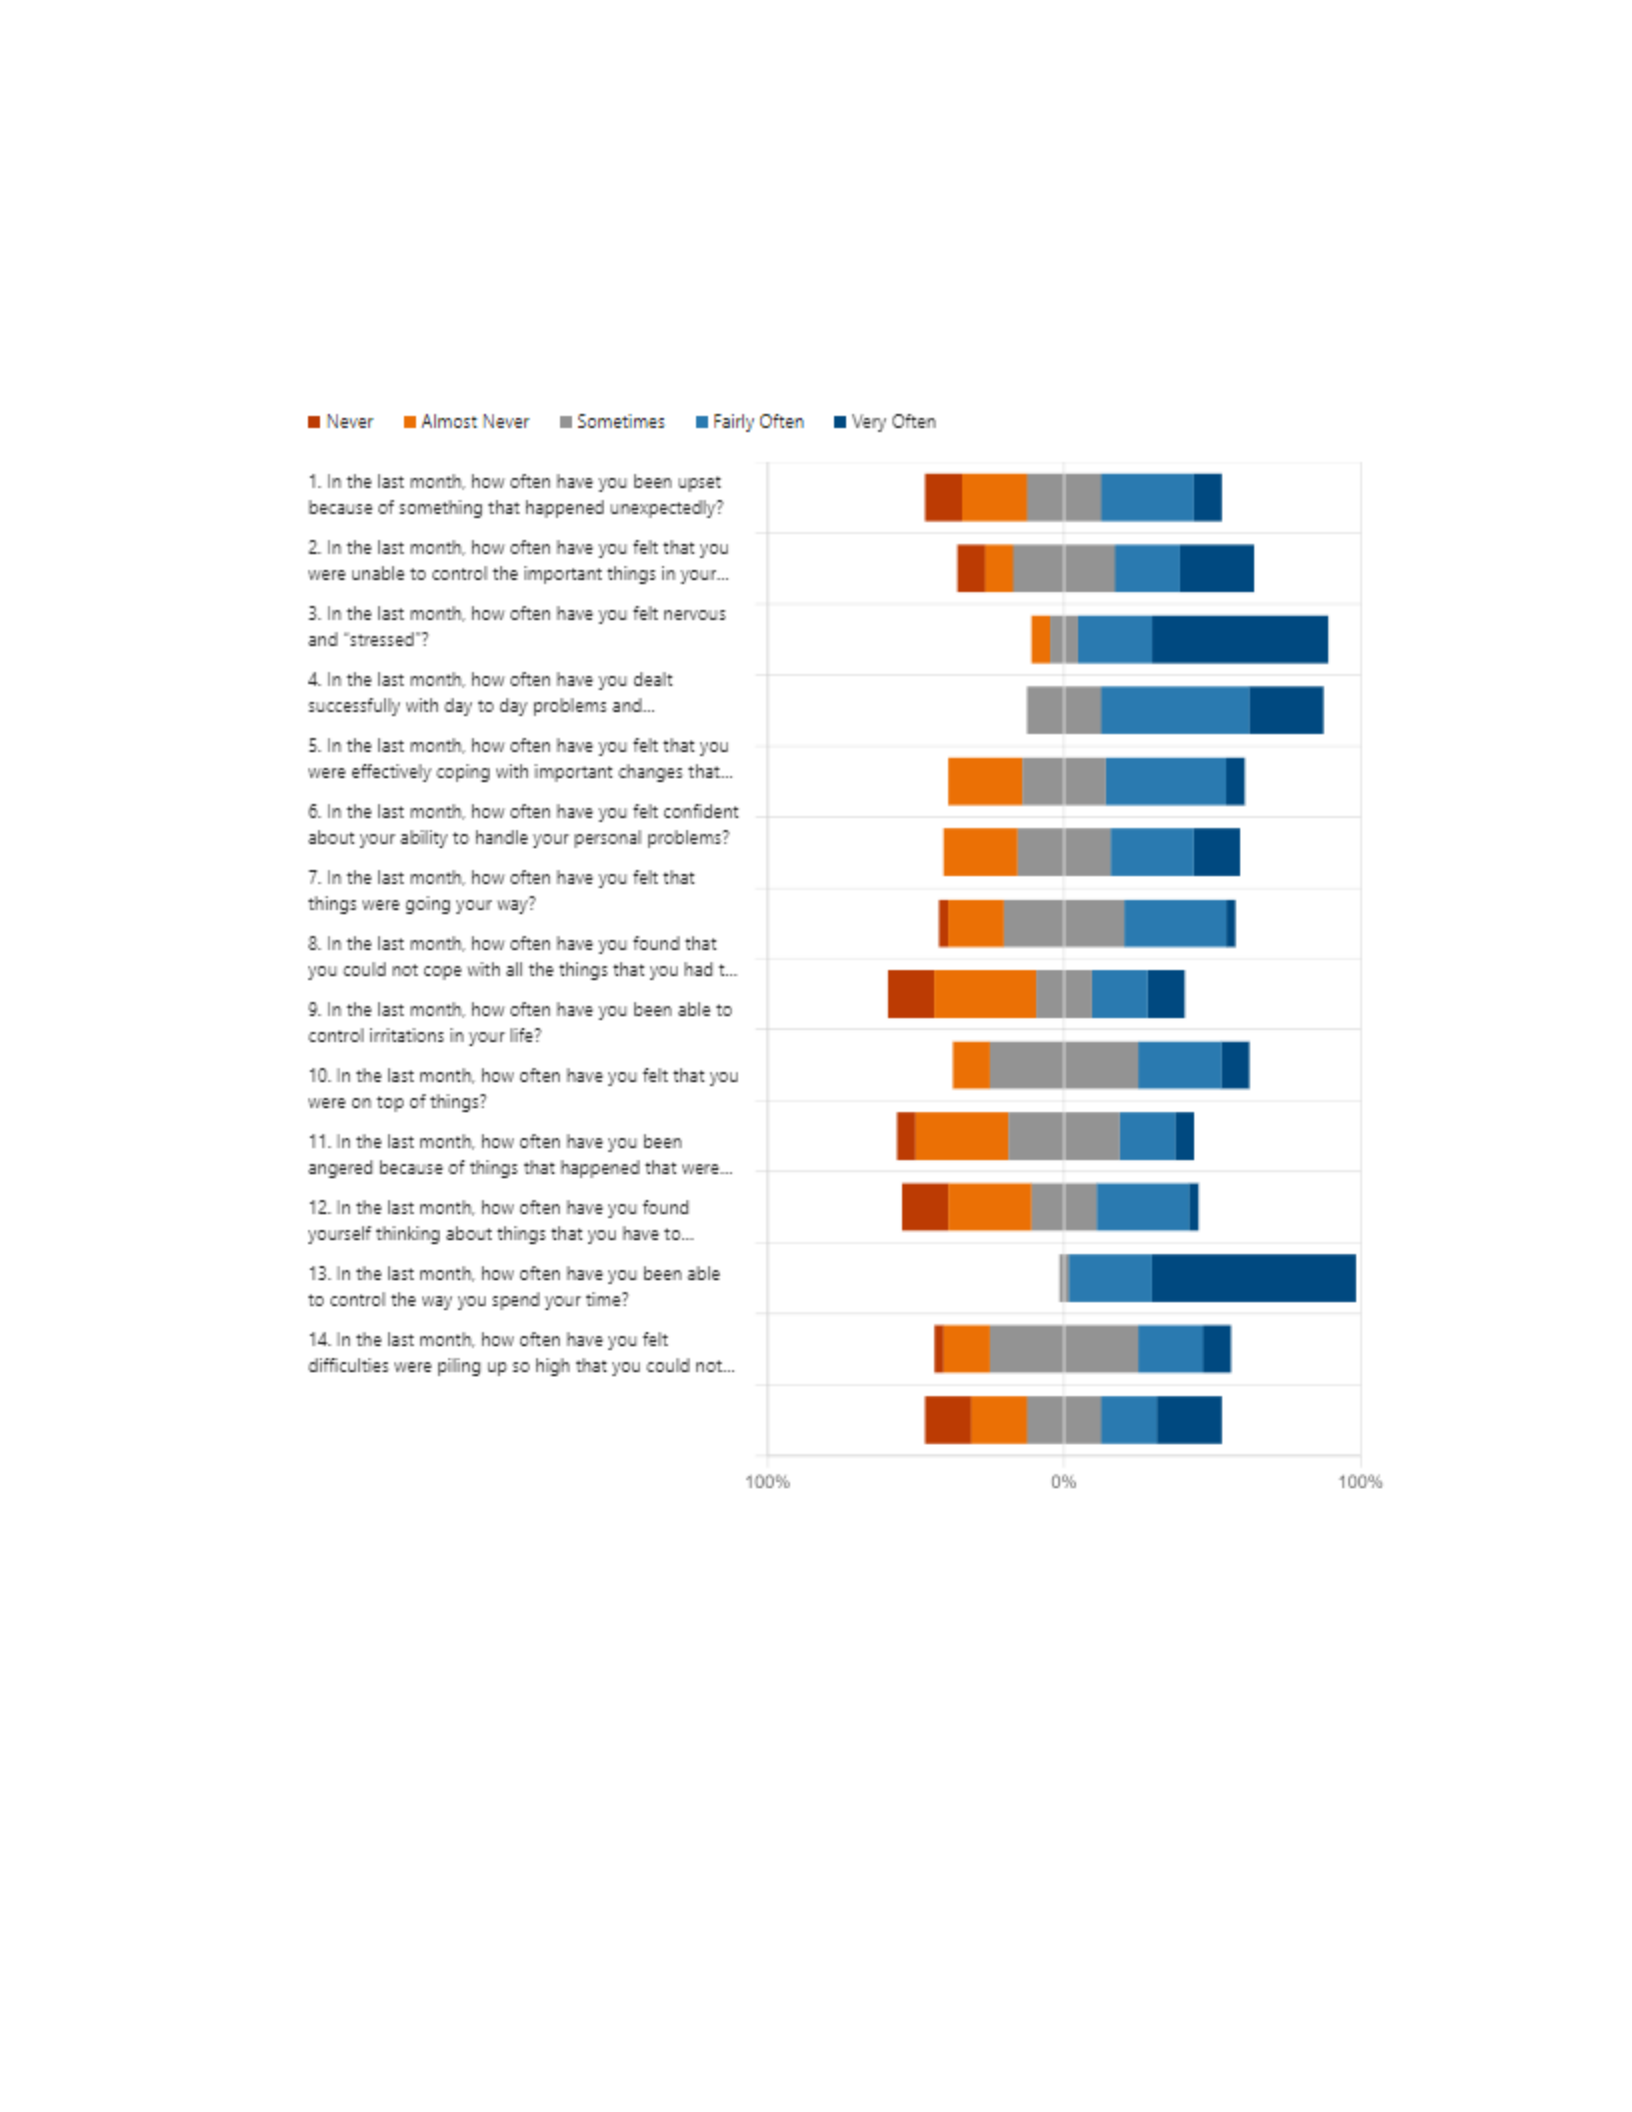
84
Figure 1
Perceived Stress Scale Presurvey Data (N = 30)
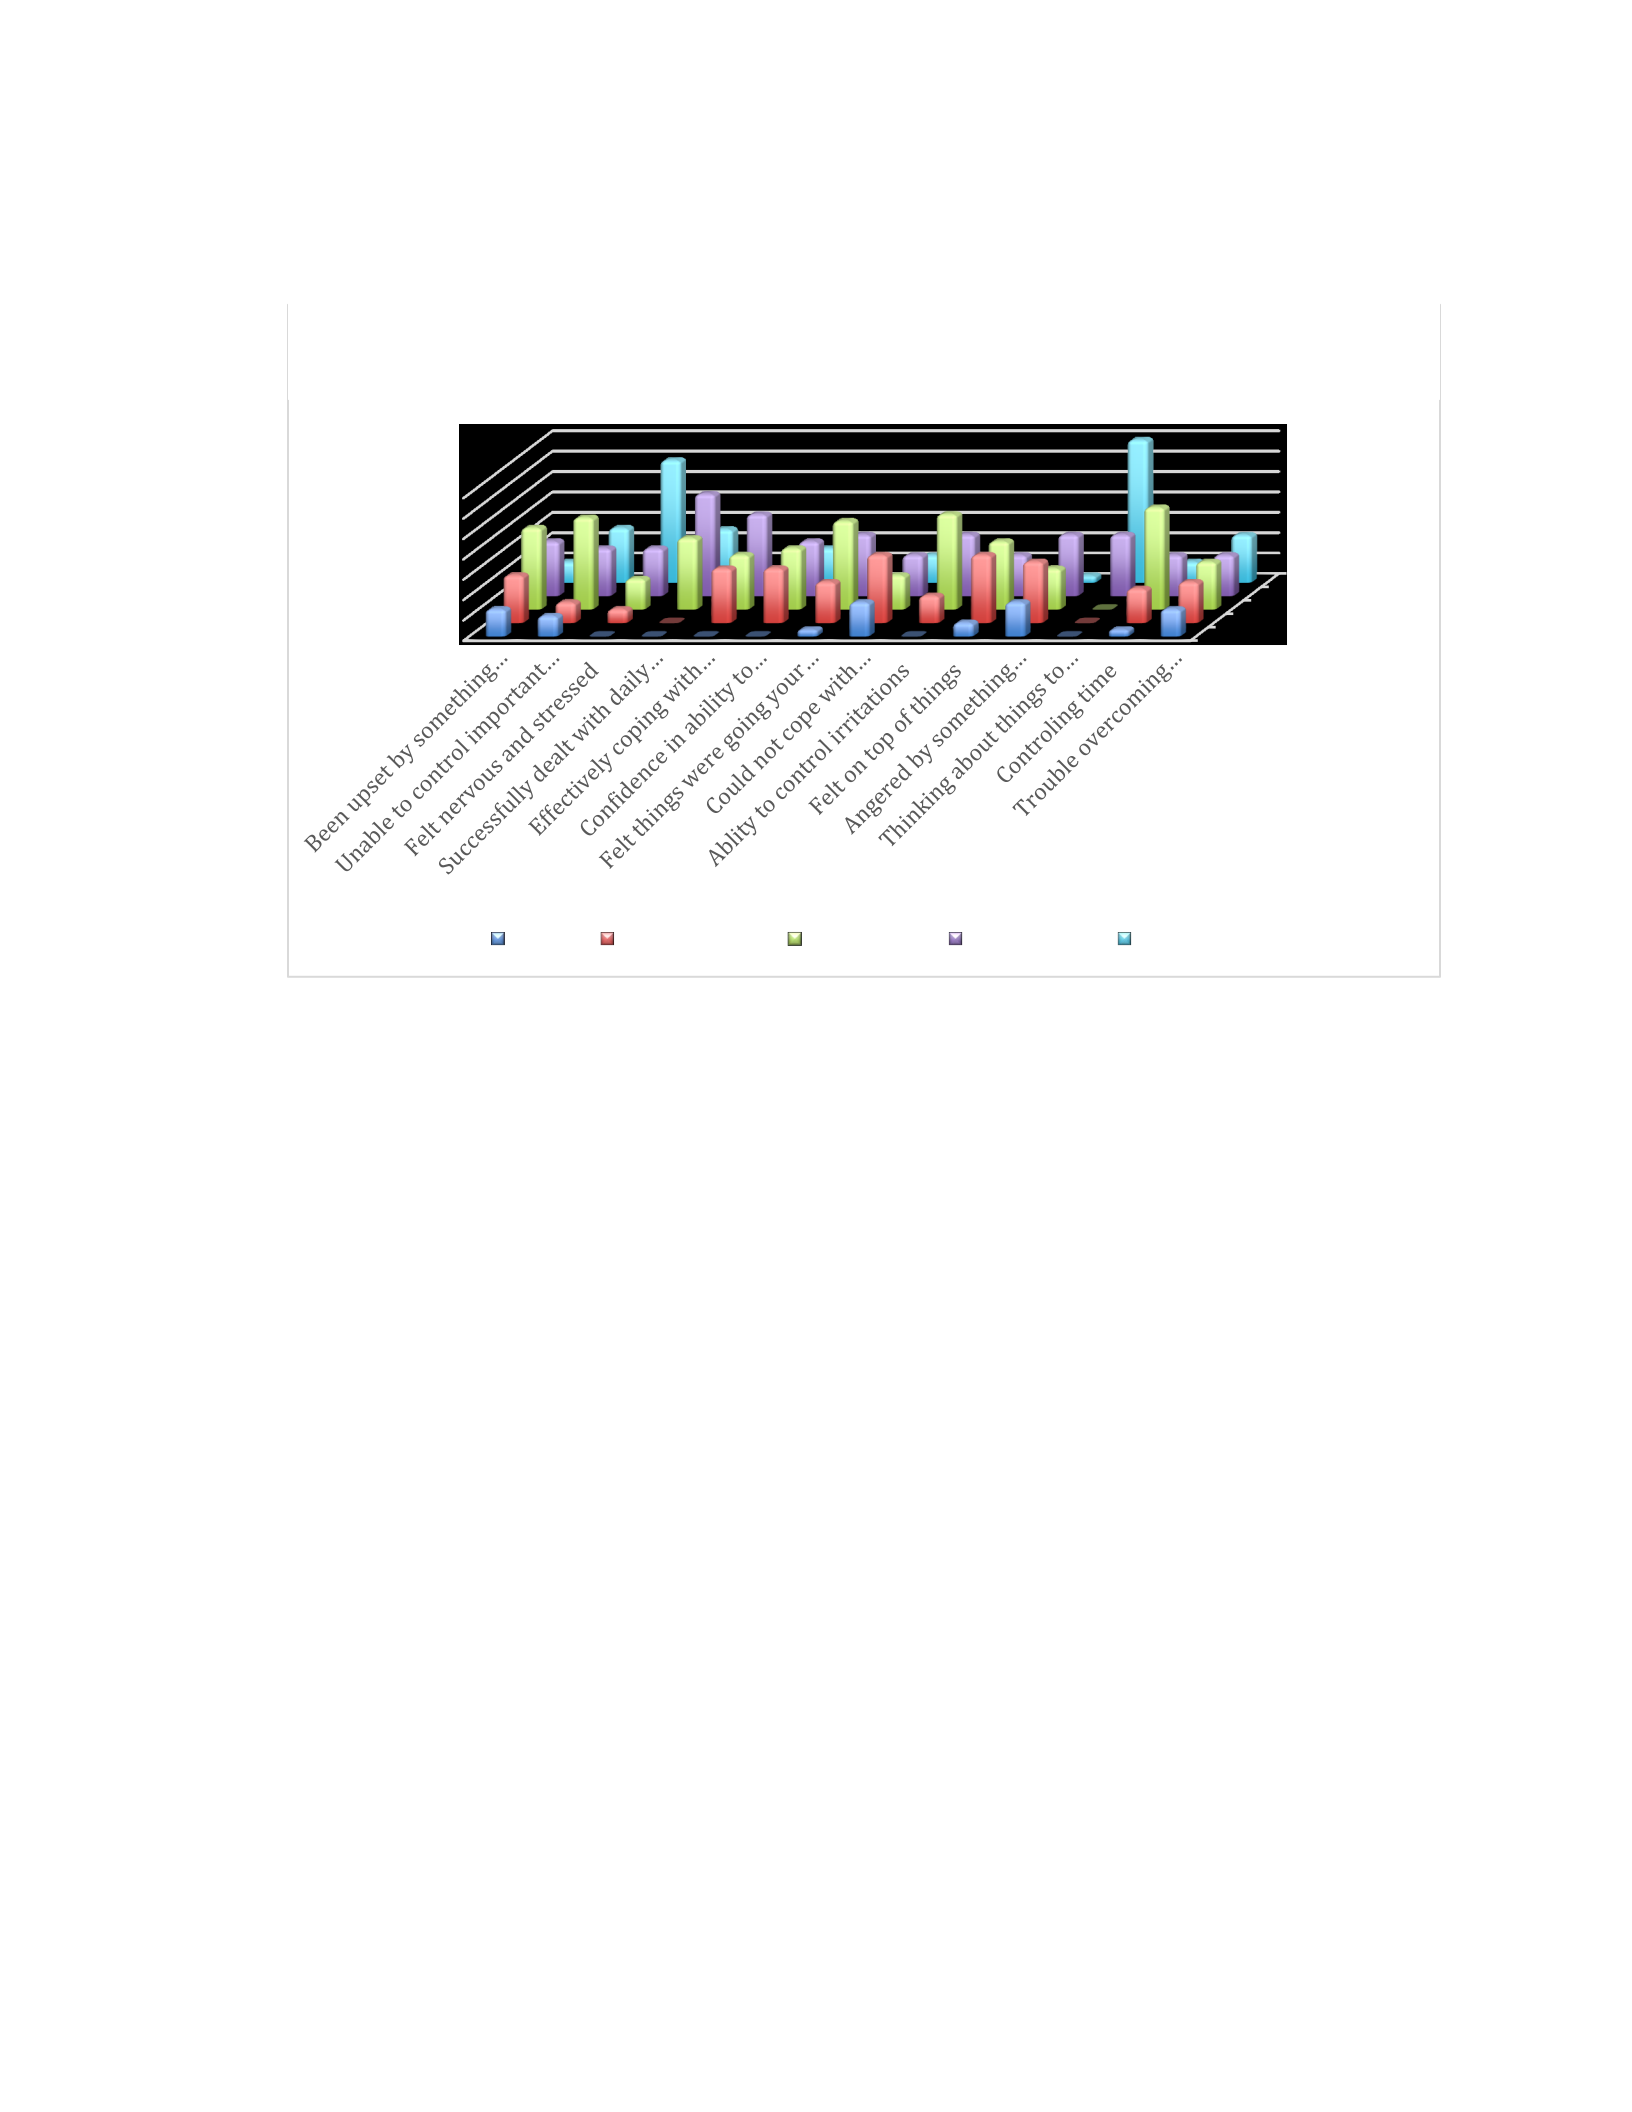
85
Postsurvey Results
The restructured format of the postsurvey was important to understand the effect
of participating in the stress management module. The postsurvey was shared with the 30
eligible participants who completed the presurvey and included the preliminary questions
that would prompt whether or not the participant could complete the PSS based on
participation in the stress management module. I found that many participants were
honest in acknowledging the number of weeks that they completed. Allowing participants
the option to move forward with submitting a postsurvey response if they complete one
or more weeks of the stress management module meant that participants who did not
participate in the module were not allowed to submit a postsurvey response, resulting in
fewer postsurvey responses. Of the 30 participants invited to submit a postsurvey
response, approximately half of the sample completed the survey. I expected this low
Never
Fairly Often
0
10
20
30
40
50
60
70
Perceived Stress Scale Pre-Survey Results
Never Almost Never Sometimes Fairly Often Very Often
Figure 2
Perceived Stress Scale Pre
survey Percentage Chart (N = 30)

86
response due to the timing of the module and postsurvey. At the discretion of the
Foundations Course Director, additional attempts to foster more participation were
discouraged. At the end of the postsurvey period, a total of 14 participants submitted a
response to the invitation to complete the postsurvey. The preliminary questions that I
added to the beginning of the postsurvey were helpful for understanding which weekly
modules were the most effective for students managing their stress. Three participants -
one female and two males - indicated that they did not participate in any of the weekly
modules. They were not part of the postsurvey analysis because they did not meet the
requirements to respond to the postsurvey. Table 3 represents the demographic
characteristics of the postsurvey sample of 11 participants.
Table 3
Demographic Characteristics of Postsurvey Sample (n = 11) by Age and Gender
Demographic characteristics
n
%
Gender
Male
4
42.86%
Female
7
57.14%
Age
18-22
0
0%
23-27
11
100%
28-32
0
0%
33-37
0
0%
38-42
0
0%
43-47
0
0%
Of the 11 participants included in the postsurvey analysis, four participants
indicated that they completed all 4 weeks of the module, while two students indicated
they participated in 3 weeks. Three participants indicated they participated in two weeks

87
of the training, while the remaining two participants only completed 1 week. Nine of the
respondents who completed 1 week or more of the stress management module completed
the Breathing Exercises in Week 2. Only six participants completed the Raisin exercise
from Week 1 and seven completed Week 3’s Body Scan and Week 4’s Walking
Meditation exercises.
Unfortunately, the number of participants who submitted a presurvey and
postsurvey response was not as proportional to the cohort as expected. Only 30 students
responded to the PSS presurvey, and 11 of those students completed all or some of the 4-
week stress management module and responded to the postsurvey. The total number of
students that submitted a presurvey response for the study did not tally up to a quarter of
the enrolled students that were invited to participate. Additionally, about half of the
students that submitted a presurvey response submitted a postsurvey response, reducing
the targeted sample size even more. The study was underpowered due to the limited
number of participants, so the results should be interpreted with caution.
The postsurvey results revealed that all 11 respondents still reported feeling
stressed to some degree after completing the stress management module. About 45% of
participants reported feeling stressed often while 36.4% indicated they felt stressed
sometimes, and 18.2% reported almost never feeling stressed. Over half of the
respondents (63.7%) indicated they continued to have issues coping effectively often
while the remainder indicated little or no issues in this area. Again, when asked about
thinking about the things they have to accomplish in the future, only 9.1% responded to
thinking about this sometimes, and the majority indicated they think about this often.
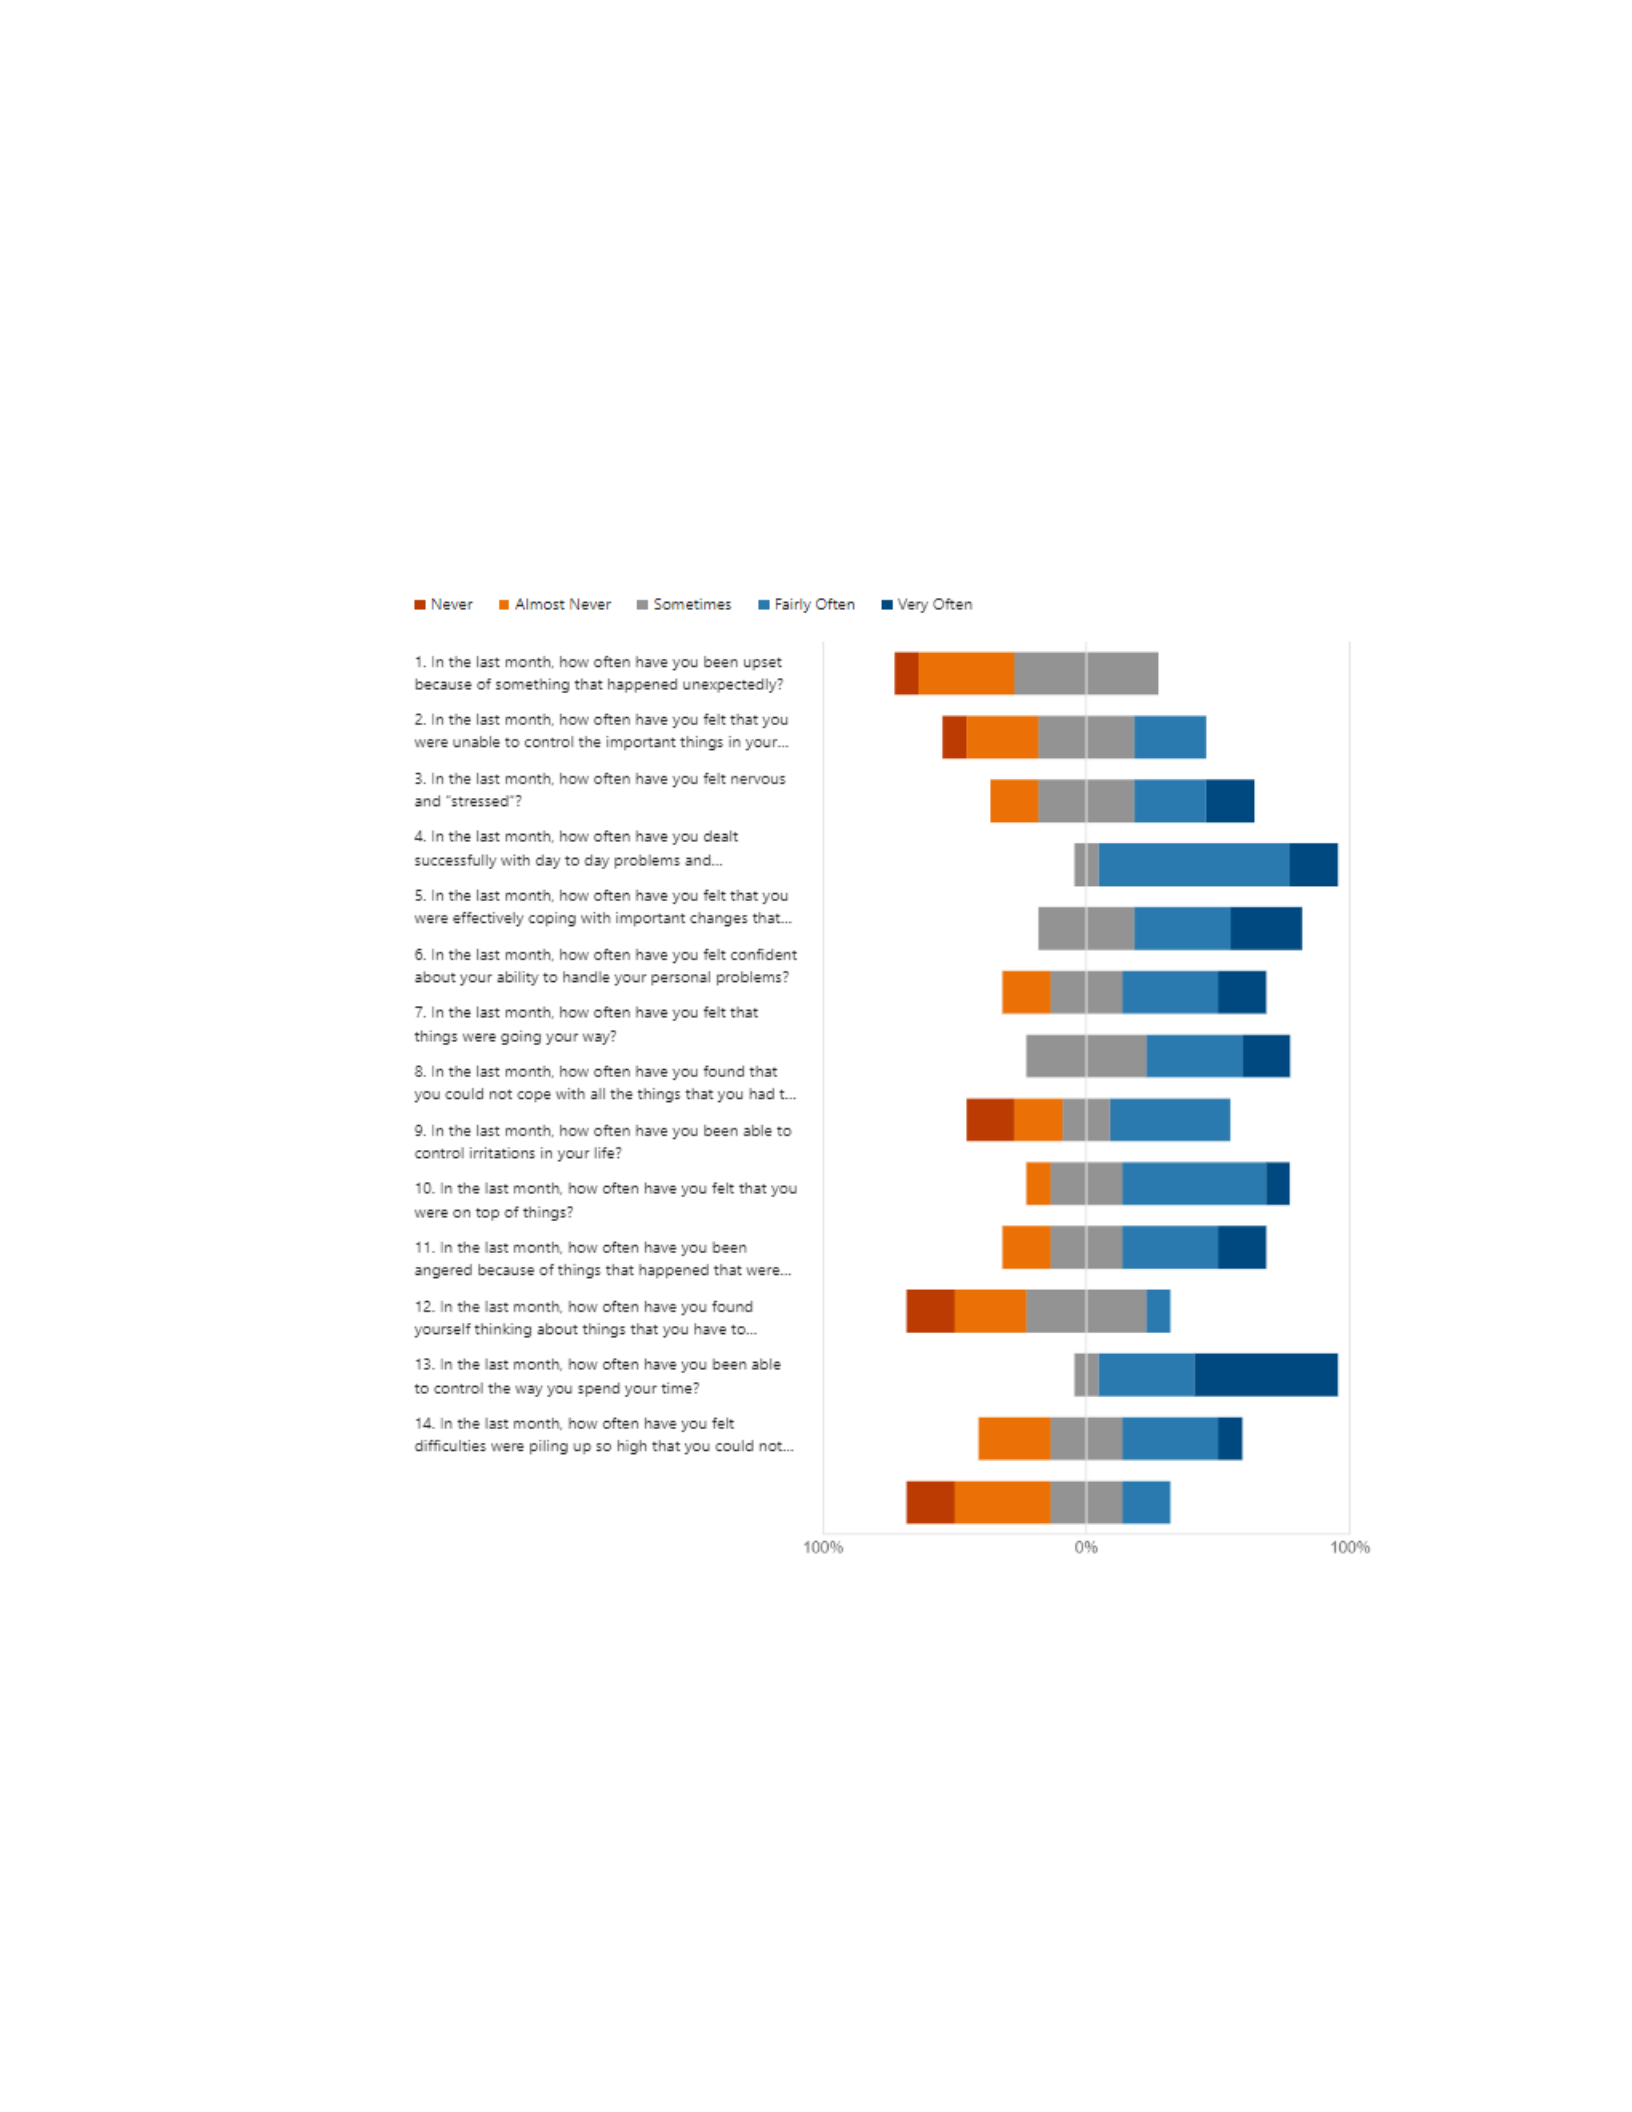
88
Based on this, the postsurvey results revealed that the participants continued to
experience stress, apprehension, or anxiety after completing the stress management
module. Figure 3 represents all the postsurvey responses.
Figure 3
Perceived Stress Scale Postsurvey Data (n = 11)
Inferential Statistics
After the conclusion of the 4-week module and collection of the postsurvey, I
analyzed the data using Version 28 of IBM SPSS Statistics. Participants were assigned a
number at random for use to quantify the data into an Excel spreadsheet. Gender was also

89
quantified as either “0” for “male” or “1” for “female”. Because presurvey and
postsurvey data were captured individually, I created a separate spreadsheet to code the
variables in one document for input for SPSS analysis. I included the participant’s
assigned number, age, gender, and the scale responses for each question in separate
columns. I used the same scale ratings from the PSS of 0 to 4 with 0 = never, 1 = almost
never, 2 = sometimes, 3 = fairly often, and 4 = very often to code presurvey and
postsurvey responses. Due to the positivity of Questions 4, 5, 6, 7, 9, 10, and 13, I coded
the questions in reverse order based on the instrument calculation instructions, with 0 =
very often, 1 = fairly often, 2 = sometimes, 3 = almost never, and 4 = never (see Cohen et
al., 1983). A total column was added to each participant’s row of responses for the sum
of the participant’s presurvey results and a total column for the sum of the participant’s
postsurvey results. Higher cumulative total scores on the PSS indicate higher levels of
perceived stress (Cohen et al., 1983).
Because I wanted to see if there was an effect of the stress management module
on the participants’ perceived stress levels and capture the completed weeks in the
postsurvey prerequisite, I added additional columns to indicate “yes” or “no” to capture
weekly module participation. I found it significantly easier to utilize dual monitors for
this process and used one screen to reference the presurvey and postsurvey data from the
data collection spreadsheet while I entered the quantified data on a new spreadsheet on
the second monitor compiling all the data into one spreadsheet. To keep track, I filtered
data collection responses by email address to ensure I was capturing the correct data for
each participant, entering each scale one by one. I left the postsurvey columns blank for

90
the participants who did not submit a response. Because this was my first time collecting
and analyzing the data, I wanted to manually enter the data for this process, taking my
time to make sure the data were accurate instead of relying on shortcuts. I ended this
process with a total of 35 columns of variables and 30 rows that included participant data
for each variable in the presurvey and postsurvey sample.
I saved the new spreadsheet to my desktop before importing the datasheet into
SPSS. In the input preview, the variables appeared to be measured correctly with the
proper variable codes assigned from nominal to scale. Once the data were loaded,
however, all the variable categories changed to nominal variables. I had to go into the
variable view to change the measure for the pre- and postsurveys to reflect ordinal
measurements. While in the variable view, I reviewed the variable labels for the dataset
to ensure the proper labels were coded. The student number variable remained unchanged
as a scale variable. Gender was also properly coded as a nominal variable, and age was
appropriately labeled as a scale variable. Additionally, I labeled the weeks of the stress
management module to reflect the activity of that week (i.e., raisin exercise, breathing
exercise, body scan exercises, and walking meditation) and verified each week was coded
as a nominal variable.
To begin the analysis, I ran descriptive statistics on the dataset to ensure
everything was captured appropriately. I also ran a t test on both samples to look at the
mean comparisons by gender and to see the standard deviations of both samples. When
reviewing the data, I noted that the data met some of the paired t-test assumptions but not
all. The analysis required the dependent variable to be measured on an interval scale for

91
reliability, which was met because the participants’ perceived stress levels – the
dependent variable - are measured on an interval scale (McCrum-Gardner, 2008).
Additionally, with a paired t-test analysis, it is necessary to compare the same pairs of
variables, as identified as the participants’ presurvey and postsurvey responses (Pandis,
2015). Because Cronbach’s alpha is commonly used in medical education research to
measure the reliability of a scale and measure error variance within a test (Tavakol &
Dennick, 2011), I used a reliability scale alpha to test the samples’ internal reliability of
the surveys. Cronbach’s alpha was α = .878 suggesting acceptable results but prompting
me to run a factor analysis. The factor analysis revealed an abnormal distribution across
the sample. I ran a compare means test on my samples to identify outliers. There were
significant outliers in the dataset from the relatively small presurvey sample size and
even smaller postsurvey sample size. Additionally, the variables were unevenly
distributed, as seen in Figure 4. All other assumptions had been met.
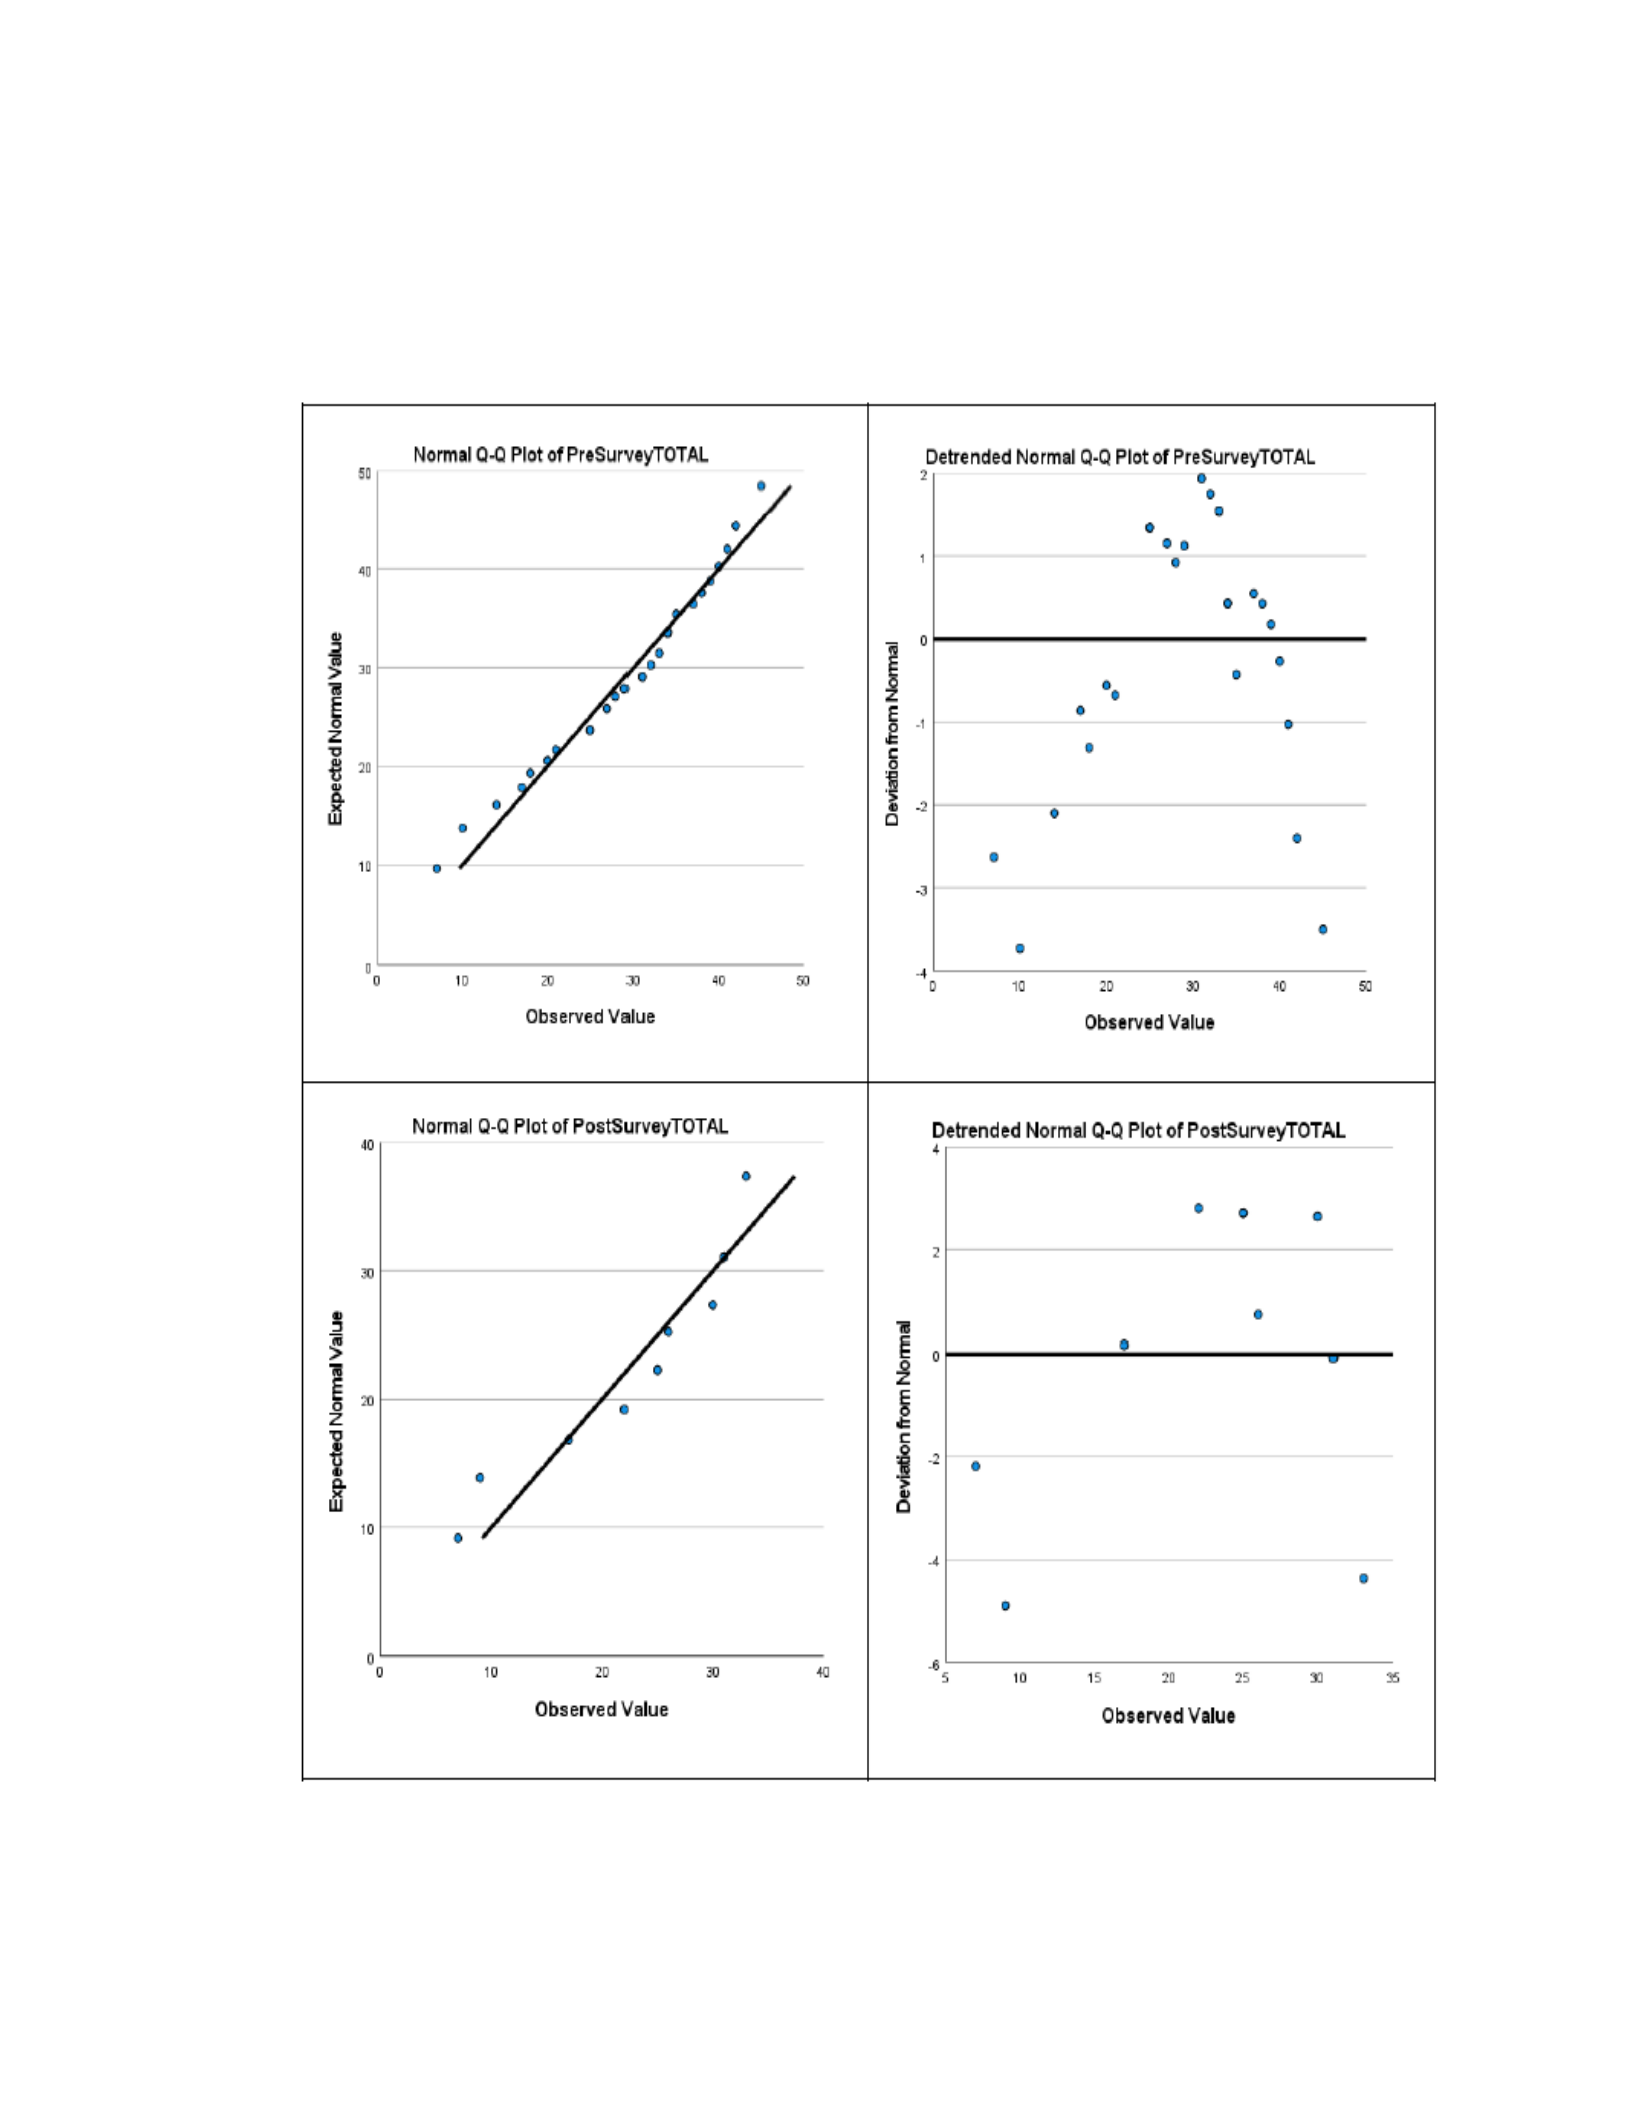
92
Figure 4
Distribution of Pre
-Survey and Postsurvey Totals

93
The study was underpowered with the sample size being too small to run a
reliable t-test analysis, therefore, I used Wilcoxon’s signed rank nonparametric test
because this test is more robust and has less statistical assumptions about the population
distribution. I chose the related-samples Wilcoxon signed rank test because it is typically
used when assumptions have not been met to compare data from the same sample or
related samples (Whitley et al., 2002). To use the Wilcoxon signed rank test, four
assumptions had to be met. The sample needed to include dependent samples to assess
pre- and posttest measurements and be independently observed (Whitley et al., 2002).
Additionally, the samples needed to include a continuous dependent variable and be
measured on an ordinal scale. All four assumptions had been met, so I proceeded with the
analysis. Using the non-parametric analysis function, I compared related samples by
comparing the medians between the presurvey totals to the postsurvey totals to generate a
Wilcoxon analysis that could answer the research question.
The Wilcoxon signed rank test revealed a statistical difference between the overall
stress scores after the intervention (Md = 25, n = 11) compared to before the intervention
(Md = 31, n = 30), z = 3.27, p = .032, confidence interval parameter estimate at 95.0%.
With this test, a medium effect size (r = .51) was found (see Field, 2015). Table 4 shows
the results of the analysis, revealing that there was an effect on first-year DO students’
stress levels after participating in a stress management module based on the
presurvey/postsurvey scores as measured by the PSS.

94
Table 4
Related-Samples Wilcoxon Signed Rank Test on Median Differences Between Presurvey
and Postsurvey Perceived Stress Scale Totals
Null hypothesis
Significance a, b
Decision
The median of
difference between
presurvey total and
postsurvey total
.032
Reject the null hypothesis
a. Significance level is .050
b. Asymptotic significance is displayed.
Relying on the related-samples Wilcoxon signed rank test, a comparison of the
presurvey and postsurvey mean differences indicated that it would be acceptable to reject
the null hypothesis, indicating that there was some effect in DO students’ perceived stress
levels after participating in the stress management module. Statistical significance was
revealed at p = .032. Due to the study being underpowered, the results should be
interpreted cautiously.
Summary
Data were collected in a prescriptive manner before the process presented a few
challenges. After obtaining the required information needed to recruit participants,
students were emailed several invitations to participate in the study. The recruitment
period that was originally scheduled for 2 weeks lasted a total of 10 weeks. Additionally,
gaining enough participants for the study was one of the biggest challenges making
obtaining a sample population large enough for a reliable study impossible. Because the
study included three parts – completing a presurvey, participation in a 4-week stress
management module, and completing a postsurvey, it was difficult to keep participants

95
actively participating in the study without making participation a requirement. Overall,
30 participants completed the presurvey, and 11 participants indicated they participated in
some or all 4 weeks of the stress management module before completing the postsurvey.
After not meeting all the assumptions for the t-test, I conducted a nonparametric
test to determine data significance. I used the related-samples Wilcoxon signed rank test
to compare the presurvey and postsurvey response median differences. With this test, I
found statistical significance (p = .032), indicating that there was an effect on first-year
DO students’ stress levels after participating in the stress management module based on
the presurvey and postsurvey scores as measured by the PSS. Because the study was
underpowered, results should be interpreted cautiously.
In the next chapter, I discuss the interpretation of findings and analyze the
findings as related to Bandura’s (1977) self-efficacy theory and Quick and Quick’s
(1984) preventive stress management theory to contribute knowledge to the field. Later, I
share the limitations of the study, focusing on the generalizability, validity, and reliability
of the study. I also share my recommendations for future research referencing the
importance of reviewing the strengths and weaknesses of the study and historical
literature before moving forward with more research. Finally, I discuss the implications
for social change before moving on to the conclusion of the entire study.

96
Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of the quasi-experimental study was to assess the effect of
participation in a 4-week stress management module on first-year DO students’ stress
levels. This study focused solely on first-year students enrolled in a DO program located
in the southeastern United States and did not contain a control group. The same sample
group of 30 participants was used to capture data using outcome measurements from the
PSS from the presurvey and postsurvey measurements.
During the hypothesis testing process, three of four assumptions for the t-test
analysis had been met. Due to the abnormal distribution of a small sample size and the
study being underpowered, I used a nonparametric test to analyze data and test the
hypothesis. I chose the related-samples Wilcoxon signed rank test to compare the means
between the presurvey totals to the postsurvey totals. The Wilcoxon signed rank test
revealed statistical significance at p = .032, indicating that there was an effect on first-
year DO students’ stress levels after participating in the stress management module based
on the presurvey and postsurvey scores as measured by the PSS, which should be
interpreted cautiously. Therefore, the null hypothesis was rejected.
Interpretation of Findings in Relation to the Empirical Research
The literature review revealed that regardless of the year of medical education,
stress was still commonly displayed in medical students (Dyrbye et al., 2013). The results
of this study reaffirm those findings by revealing that medical students continue to
experience stress. This study, however, contributes to the knowledge by adding a
component that incorporated DO students’ stress levels because former research seemed

97
to focus on MD students’ stress levels. The difference between the DO and MD programs
is the holistic approach to medicine which serves as the foundation of osteopathic
principles and practice (American Osteopathic Association, 2019).
Additionally, this study confirms that a stress management program was helpful
for DO students’ stress levels as an effect was seen in perceived stress scores after
participating in the stress management module. Researchers had previously found that
stress management programs were beneficial for reducing medical students’ stress levels
and enhancing quality of life, professionalism, and mental health by providing students
with the skills they need to manage and deal with stress (Dyrbye et al., 2013; Kushner et
al., 2011; Polle & Gair, 2021). Research also showed that voluntary stress management
programs had been consistently studied and shown effective for reducing medical
students’ stress levels (Dabrow et al., 2006; Greeson et al., 2015; Henning et al., 2011),
and this study also supports former research in that the 4-week stress management
module was a voluntary program offered to first-year DO students. Participants in this
study were encouraged to volunteer to participate in the module, especially if they self
identified as being stressed.
Interpretation of Findings in Relation to the Theoretical Frameworks
Lastly, this study was grounded using two theoretical frameworks: Bandura’s
(1977) self-efficacy theory and Quick and Quick’s (1984) preventive stress management
theory. Bandura’s self-efficacy theory suggests that coping techniques can alter and
sustain the strength of an individual’s self-efficacy. This theory also suggests that with
consistent practice, self-efficacy is enhanced through repetitive tasks and the ultimate

98
mastery of the content (Bandura, 1977). Quick and Quick’s theory of preventive stress
management suggests that early recognition of stress along with the early implementation
of measures to reduce and manage stress are considered beneficial. The results of the
study confirm Bandura’s self-efficacy theory, as well as Quick and Quick’s theory of
preventive stress management. The study participants’ perceived stress scores were
altered through the use of consistent stress management practices that were shared each
week during the 4-week module. Study participants were encouraged to repeat the
module exercises as many times as needed to their benefit.
Limitations of the Study
When planning the study, several limitations had been identified. Limitations of
the study sample included research showing that matriculating students already
experienced more stress than the general population due to preparation for medical school
(Anandhalakshmi et al., 2016). Additional research design limitations included collecting
data from one study site and using only one group of participants when other cohorts
could have benefited from participating in a stress management module, minimizing the
generalizability of the study. Exclusionary criteria included students from different
cohorts and first-year students enrolled in other programs offered by the college.
Additionally, because this study was concentrated on students from one DO school, the
results were not generalizable for other medical schools or for schools that offer multiple
health professions programs. A larger sample size would have been preferred to test the
generalizability of the stress management module effects. Also, because there was
minimal information available on this specific topic, it was unknown whether the

99
osteopathic principle of whole-body practice influenced DO students’ mindset on stress
and well-being. Further limiting the study design was the self-reported data from
participants, subjecting the study to response bias. At the end of the 4-week stress
management module, participants were asked to indicate which stress management
activities they completed before being able to complete the PSS postsurvey. Of the 11
PSS postsurvey respondents, only four participants indicated that they participated in all
4 weeks of the module while the remaining seven participants completed 3 weeks or less
of the training. Ethical procedures for collecting and reporting data were followed as
reasonable measures to address the identified limitations.
The major limitation identified from the execution of the study was timing within
the semester, which yielded less participation than anticipated. The study was planned to
take place during the Fall semester, which eased first-year DO students into the
curriculum at a slower pace. The study was executed towards the end of the Spring
semester, which was structured differently from the Fall semester with more curriculum
being covered at a faster pace. Although study participants had successfully completed
one full semester of the medical school curriculum, the sample of participants was
already inundated with the stress of an eventful Spring semester when the study was
executed. The small number of participants underpowered the study, so the results should
be interpreted carefully when reviewing.
Recommendations
The results from this study, which should be interpreted cautiously, showed that
there was an effect in stress management for those who completed all or part of the

100
module, indicating a short 4-week stress management module could be beneficial to more
DO students in the future. One recommendation is to embed the module into a course,
making it a requirement for students to participate in all 4 weeks. Researchers have
already suggested that medical schools make stress management training a requirement
for their medical students by incorporating it into the curriculum (Brennan et al., 2016;
Hathaisaard et al., 2022; Pohontsch et al., 2018; Yang et al., 2018). I would also
recommend that the module be facilitated by either a foundations course director, an
academic support counselor, or an external party to guide the exercises and facilitate
participation (Dyrbye et al., 2011; Yusoff et al., 2013). Also, by structuring the stress
management module into a course, the curriculum team may be better able to determine
where it fits best for students timewise and pinpoint a point in time when students might
benefit most from it.
Implications for Positive Social Change
Because DO students experienced an effect in their stress levels after participating
in the stress management module, this study has the potential to affect positive social
change at the individual and organizational levels. Research has shown stress
management as an effective tool in general (Dhandapani et al., 2022; Norphun et al.,
2020). Research has also shown stress management effective for medical students and
residents (Kakoschke et al., 2021; Polle & Gair, 2021). The implications of this study
support the research and could be beneficial for DO students who participate in the stress
management module if offered by the institution. Additionally, the medical school could
benefit from offering a stress management module and could potentially use the stress

101
management module as a marketing tool during recruitment by showing prospective
students that a mechanism to cope with stress is in place to help assist students while
enrolled in medical school.
Individual Implications
Participating in a stress management module has the ability to affect DO students’
stress levels on an individual level by providing stress management tools for students to
use at any time. This study’s stress management module incorporated several techniques
from mind-body awareness to breathing and walking exercises. The module’s exercises
also included a variety of lengths each week to allow the student to complete the exercise
whenever a free moment presented itself, generating the flexibility DO students needed to
fit something else into their schedules. These small chunks of time for stress management
could easily fit into a DO student’s schedule and be done anywhere with no physical
tools required and only requiring time to complete the exercise and very little guidance.
Participants were also encouraged to complete the weekly exercises as many times as
they felt were necessary each week to cope with their stress. Learning the stress
management exercises that were shared along with an understanding of how the exercise
works, DO students could take these stress management skills with them as they progress
through all 4 years of the program, into residency and post-graduate training years, and
beyond as practicing physicians. Additionally, the stress management techniques can be
used outside of medical school and could be applied and referenced in a general public
setting.

102
Organizational Implications
The organizational implications for social change in a DO school include having a
stress management module available to students to address DO students’ stress levels.
Since stress had been identified as one of the leading factors contributing to student
burnout and thoughts of dropping out of medical school (Dyrbye et al., 2019; Dyrbye et
al., 2010; Ehring et al., 2021), having preventive stress measures in place could be
beneficial for the institution’s retention and attrition rates. Additionally, offering a stress
management module to students could be positively perceived by current and prospective
DO students as it shows administration cares about students’ well-being and success by
offering a complimentary resource while students are completing the program.
Methodological, Theoretical and Empirical Implications
This study showed that with consistent practice, DO students’ perceived stress
could be changed, supporting Bandura’s (1977) self-efficacy theory. Additionally, this
study supported Quick and Quick’s (1984) theory of preventive stress management by
showing how immediate stress management was effective for managing stress. Although
the study was intended to be implemented during the Fall semester, implementing the
stress management module in the Spring semester before final exams was the prime
opportunity to offer the stress management module when the DO students could benefit
most from learning new stress management techniques. Regardless of timing, however,
the stress management module contributes to the research by adding that DO students
found that participating in a 4-week stress management module had an effect on their
stress levels.

103
Recommendations for Future Research
This study could be replicated in conjunction with the former research, guidance
from Chapter 3, and the appendices. However, it is recommended that future researchers
consider the limitations of the study before moving forward. Researchers may offer a 4-
week stress management module to students enrolled in a DO program or any similar
health professions field. For this study, the stress management module was only offered
to first-year DO students, but all students in the program could have benefited from
participating in the study. To garner the most effect, I recommend that the stress
management module be offered before any high-stress time (i.e., matriculation or before
final exams) while the participants are enrolled in the program of study. Additionally, I
recommend that future research incorporate a requirement for module participation by
embedding the module into the curriculum and have the module facilitated by a course
director or wellness instructor. A Foundations, Introduction, or Well-Being course in any
health professions program would serve well for this need. Additionally, researchers may
elect to offer the 8-week stress management module for a longer duration and greater
exposure to stress management techniques.
Conclusion
In conclusion, the research showed that participation in a stress management
module had an effect on first-year DO students’ stress levels. Applying Bandura’s (1977)
self-efficacy theory to the study and designing the research to have participants rate their
self-efficacy through a pretest and posttest design revealed that participants were able to
enhance their self-efficacy through persistent stress management practices. The

104
implementation of the stress management intervention also occurred during a time when
the participants could benefit from having stress management techniques shared with
them, further supporting Quick and Quick’s (1984) theory of preventive stress
management and demonstrating that implementing immediate stress management
techniques is effective for managing stress.
The results of this study, which should be interpreted with caution, support
previous research by revealing that medical students continue to report high stress levels
and highlighting the need to offer stress management techniques to medical students.
This study, however, acknowledges the gap that DO students were not explicitly
identified in former research and contributes knowledge to the field in that the study
specifically addresses stress management effects on DO students’ stress levels.
Understanding that the DO approach to medicine conceptualizes that patients are treated
holistically, DO students still experienced high stress and could benefit from participating
in a stress management module. From this study, participating in a short 4-week module
had an effect on the DO students’ stress levels.

105
References
Abdelsalam, N. M., & Said, R. M. (2022). Level and predictors of mental health literacy
of depression and suicide among undergraduate medical students. Middle East
Current Psychiatry, 29(1), 1-8. https://doi.org/10.1186/s43045-022-00229-6
Abramova, T., Ogunji, A., & Taiwo, O. O. (2015). Assessment of depression and stress
among medical students from three different countries: Nepal, Ukraine and
Russia: A cross-sectional survey. International Journal of Preventive and Public
Health Sciences, 1(2), 9-13. https://doi.org/10.17354/ijpphs/2015/10
Abrams, M. P., Salzman, J., Rey, A. E., & Daly, K. (2022). Impact of providing peer
support on medical students’ empathy, self-efficacy, and mental health stigma.
International Journal of Environmental Research and Public Health, 19(9), 1-13.
https://doi.org/10.3390/ijerph19095135
Agarwal, A., Al-Zharani, H. A., & Shah, S. S. (2020). Resilience and burnout: Relation
of emotional intelligence (EI) and stress management capabilities among health
professional students of Northern Border University – Arar, Kingdom of Saudi
Arabia. Pakistan Journal of Medical and Health Sciences, 14(1), 425-429.
https://pjmhsonline.com/2020/jan_march/pdf/425.pdf
Aherne, D., Farrant, K., Hickey, L., Hickey, E., McGrath, L., & McGrath, D. (2016).
Mindfulness based stress reduction for medical students: Optimising student
satisfaction and engagement. BMC Medical Education, 16(209), 1-11.
https://doi.org/10.1186/s12909-016-0728-8
Al Raddadi, W., Aljabri, J., Kareem, M., Alattas, A., & Alkhalawi, M. (2017). The

106
prevalence of depression and anxiety among medical students in comparison with
non-medical students: A cross-sectional study in Taibah University, All Madinah
Al Munawwarah, Saudi Arabia. International Journal of Academic Scientific
Research, 5(1), 72-80. https://www.ijasrjournal.org/wp-
content/uploads/2017/03/MS26XXV.pdf
American Association of Collegiate Registrars and Admissions Officers. (2016). Student
displacement: A guide for higher education administrators. American Association
of Collegiate Registrars and Admissions Officers.
American Psychiatric Association. (2014). Diagnostic and statistical manual of mental
disorders. American Psychological Association.
American Osteopathic Association. (2019). About us. https://osteopathic.org/about/
Anandhalakshmi, S., Sahityan, V., Thilipkumar, G., Saravanan, A., & Thirunavukarasu,
M. (2016). Perceived stress and sources of stress among first-year medical
undergraduate students in a private medical college. National Journal of
Physiology, Pharmacy and Pharmacology, 6(1), 9-14.
https://doi.org/10.5455/njppp.2015.5.1909201574
Aulia, F., Hastjarjo, T. D., Setiyawati, D., & Patria, B. (2020). Student well-being: A
systematic literature review. Buletin Psikologi, 28(1), 1-14.
https://doi.org/10.22146/buletinpsikologi.42979
Ayala, E. E., Winseman, J. S., Johnsen, R. D., & Mason, H. R. C. (2018). U.S. medical
students who engage in self-care report less stress and higher quality of life. BMC
Medical Education, 18(189), 1-9. https://doi.org/10.1186/s12909-018-1296-x

107
Bandura, A. (1977). Self-efficacy: Toward a unifying theory of behavioral change.
Psychological Review, 84(1), 191-215. https://doi.org/10.1037/0033-
295X.84.2.191
Bandura, A. (1978). The self system in reciprocal determinism. American Psychologist,
33(4), 344–358. https://doi.org/10.1037/0003-066X.33.4.344
Bandura, A., Adams, N. E., Hardy, A. B., & Howells, G. N. (1980). Tests of the
generality of self-efficacy theory. Cognitive Therapy and Research, 4(1), 39-66.
https://doi.org/10.1007/BF01173354
Baumeister, H., Reichler, L., Munzinger, M., & Lin, J. (2014). The impact of guidance on
internet-based mental health interventions — A systematic review. Internet
Interventions, 1(4), 205-215. https://doi.org/0.1016/j.invent.2014.08.003
Bhagat, V., Haque, M., Simbak, N. B., & Husain, R. (2018). Stress among medical
students and the advantages of metallisation therapy in general: A review of
literatures. Advances in Human Biology, 8(2), 59-63.
https://doi.org/10.4103/AIHB.AIHB_62_17
Bohlen, L., Shaw, R., Cerritelli, F., & Esteves, J. (2021). Osteopathy and mental health:
An embodied, predictive, and interoceptive framework. Frontiers in Psychology,
12, 1-22. https://doi.org/10.3389/fpsyg.2021.767005
Bramness, J. G., Fixdal, T. C., & Vaglum, P. (1991). Effect of medical school stress on
the mental health of medical students in early and late clinical curriculum. Acta
Psychiatrica Scandinavica, 84(4), 340-345. https://doi.org/10.1111/j.1600-
0447.1991.tb03157.x

