


1
Chapter 1: Introduction to the Study
Globally, the mortality rate among children less than 5 years dropped to 39% from
50% per 1,000 live births (United Nations Inter-Agency Group for Child Mortality
Estimation [UN IGME] & United Nations Maternal Mortality Estimation Inter-Agency
Group [UN MMEIG], 2019). Despite substantial progress in child survival overall, huge
disparities still appear between regions; for instance, in 2018, more than 82%, 8 in 10 of
the global burden of mortality among children under 5, reside in Sub-Saharan Africa
(SSA) (54%) and South Asia (28%) (UN IGME & UN MMEIG, 2019). As these figures
indicated, globally, SSA and South Asia respectively account for the highest death rates
among this age group. Between 60 and 125 of every 1,000 newborns have died before
reaching 5 years of age in 28 nations, including: Afghanistan, Haiti, SSA countries, and
Pakistan (United Nations, Department of Economic and Social Affairs, Population
Division, 2019). Comparatively, in 2019, an Australian/New Zealand child under the age
of 5 is 20 times more likely to survive than an SSA child (United Nations, Department of
Economic and Social Affairs, Population Division, 2019).
Côte d’Ivoire, located in West Africa (SSA), was classified among the 79 nations
with the highest under-5 mortality rate (U5MR) in 2016 and still lag behind expectation
with 92 per 1000 live birth U5MR (The World Bank Group, 2018).
Additionally, while the average 2019 U5MR for SSA was 76 per 1000 live births
(The World Bank Group, 2021), Cote D’Ivoire still had a relatively higher U5MR of
about 79 per 1000 live births in 2019 (The World Bank Group, 2021).

2
In exploring factors influencing death among children under 5, the literature has
revealed that lack and limitation of water and proper sanitation, as well as subsequent
contributing factors including lack of proper hygiene, were among predictors repeatedly
linked to the high death/diseases rates in childhood, mainly in disadvantaged regions of
Latin America, Africa, and Asia (Angoua et al., 2018; Darvesh et al., 2017; United
Nations Development Program, 2019; The World Bank, 2019). While 1.1 billion
individuals do not have access to potable water, 38 million reside in the Middle East, 49
million in Latin America, and 314 million in SSA. According to the United Nations
Development Programme (2019), 700 million individuals live in water-stretched nations
(i.e., Latin America, Middle East, and SSA) and are predicted to rise to 3 billion by 2025.
This dramatic situation presents a critical threat and risk for the life of children who live
in these regions, with children expected to face crucial vulnerabilities induced by lack or
incapacity (Pink, 2013). The scarcity of clean water and basic sanitation services affects
the lives of more than 40% of individuals globally (The United Nations Development
Programme, 2019). In Côte D'Ivoire, more than eight million people (about 43% of its
population) lack adequate sanitation facilities, and more than four million still use unsafe
drinking water sources, particularly in rural areas (UNICEF Côte D’Ivoire, n. d.).
Globally, about 5.6 million children less than 5 years old died in 2016 (World Health
Organization (WHO, 2018). The lack of these substantial and vital elements exposed
millions of children to illnesses associated with water, sanitation, and hygiene (WaSH)
and subsequently leading to preventable death. Each day, more than 800 children die, and
this mortality is attributed to preventable illnesses associated with poor WaSH (UNICEF,

3
2019b). In fact, many of these children die each day from diarrhea and other illnesses
mainly led by lack and/or improper sanitation and water sources (UNICEF Côte D'Ivoire,
n. d).
As aforementioned, the present research focused on children under 5 in Côte
D’Ivoire, West Africa, with their burdens associated with limitations in basic needs
including clean water, adequate sanitation, and hygiene. This study may lead to positive
social changes with further understanding of the strength of association between WaSH
and U5MR in Cote D’Ivoire by providing program planners, public health practitioners,
and governmental agencies important insights for designing targeted strategies and
programs to tackle the problem the priority population faces. Finally, such insights could
inform decision making for further planning and to design effective upstream
populationbased strategies to alleviate the health burden of the local population in Côte
D’Ivoire. In the next section, I provide the background for the study with a brief review
of the literature in support of WaSH and other factors that may influence the health and
mortality of children less than 5. I also incorporate the research questions, the problem
statement, the conceptual framework, the definitions of terms, the purpose of the study,
the nature of the study, significance, assumptions, scope and delimitations, and summary.
Background of the Study
Access to good WaSH conditions (i.e., toilets, potable water, and proper hygiene)
is essential for child development, health, and survival (Adebowale et al., 2017; Alemu,
2017; Darvesh et al., 2017; Fink et al., 2011). As the WHO/UNICEF/World Bank
group/United Nations (2015) asserted, child mortality is a key indicator used by many

4
countries around the world to evaluate the health and well-being of their children
(Adebowale et al., 2017). The literature about WaSH and U5MR highlighted the
magnitude of the problem, its significance, and the social determinants of the target
population health (e.g., socio-economic, and social burden associated with high
disparities based on geographic setting and socio-economic conditions). Globally, lack
and limitation of water affect more than 40% of the population, an alarming figure that is
expected to increase with the effect of global warming (United Nations Development
Programme, 2019).This alarming public health problem induces a serious threat to the
life of the local population, most particularly, children (United Nations, 2019). Previous
studies have shown a correlation between clean water, adequate sanitation, child health,
and survival (Alemu, 2017; Bohra et al., 2017; Cairncross et al., 2010; Pink, 2013; World
Health Organization, n. d.). Each year, the inability to access water takes the lives of
more children than the total mortality attributed to Malaria, Measles, and HIV/AIDS
(Pink, 2013). From a human security perspective, sanitation, water, and child health have
a critical linkage with child health. For instance, open sewage and inadequate sanitation
facilities severely contaminate water supplies, leading to death and illnesses (Pink, 2013).
In further exploring what factors have led children under 5 to be more affected by
premature death and associated diseases, the literature suggested that prominent
attributable factors include limited resources, lack of clean water, appropriate hygiene,
and sanitation as well as socio-economic and socio-demographic variables (Alemu, 2017;
Angoua et al., 2018; Darvesh et al., 2017; Pink, 2013; United Nations Development

5
Programme, 2019). Socioeconomic conditions, geographic areas, and socio-political
crises, for instance, affect the population through WaSH and related morbidity and
mortality (Angoua et al., 2018). For example, the increasing urbanization rate, the recent
civil war, and the rural exodus of the population in Abidjan have had a significant impact
on the population’s well-being and overall health. Particularly, the 2002 social crisis and
subsequent rural exodus have increasingly led to the formation of informal and
unplanned settlements. Most often, such informal places lack basic urban facilities (e.g.,
waste collection, water, and sanitation; Angoua et al., 2018). Additionally, the rural
exodus is associated with extreme poverty of rural habitants; consequently, they often
move from rural zones into urban zones for means of a better life. Conditions of life,
access to water, sanitation, and infrastructures are bad in rural places compared to cities
(WHO, UNICEF, 2014). With regards to the geographical factors (such as rural versus
urban) and WaSH, in spite of remarkable progress, both uneven and steady, 96% of the
global populations were using improved drinking water sources in 2015 versus 84%
(urban and rural respectively), while 82% of the urban global populations were using
improved sanitation facilities versus 51% in rural populations (urban and rural
respectively; Darvesh et al., 2017). This situation affects the health of the exposed urban
vulnerable population as exemplified in previous studies in Cote D’Ivoire by Angoua et
al. (2018). In their study, the authors suggested that various flaws in the management of
sanitation and water systems trigger the life and health of exposed local habitants to
diseases linked to WaSH conditions e.g., diarrhea, malaria, typhoid, and fever. Despite
great strides to mitigate the issue, reaching the expected targets still is slow. Angoua et al.

6
suggested a further understanding of the economic, demographic, and social predictors to
accessing
sanitation and water facilities in these places to alleviate this problem holistically and
sustainably, hence minimizing risky conditions. Diarrhea is one of the main risk factors
for deaths and illnesses among children below 5 (Darvesh et al., 2017). Despite all the
progress to reduce diarrhea-related death, incident diarrhea and related mortality still
varied and were found to be unequally distributed among regions and between SES
(Darvesh et al., 2017).
Scaling up and promoting targeted interventions e.g., access to improved
sanitation facilities, provision of safe water, and hygiene education could substantially
decrease incident diarrhea in young children. Limitations in accessing clean water and
sanitation affect incident diarrhea and related mortality in developing nations. In addition,
diarrhea is one of the main causes of death among children below 5 (Clasen, et al., 2014;
Darvesh et al., 2017). In the early twentieth century, childhood mortality was prioritized
in the health debates. Policymakers and health professionals have prioritized childhood
health outcomes to fight the increasing mortality in childhood (Adebowale et al., 2017).
Not only has this interest been extended worldwide, but it has also led to craft strategies
to halt the under-5 mortality by 2/3 between 1990 to 2015, based on the Millennium
Development Goals (MDGs; Adebowale et al., 2017).
Following the above needs and urgency to address the issue, The Millennium
Development Goal 4 (MDGs4), since its introduction, aims at reducing the U5MR by 2/3
from 1990 to 2015 (United Nations, 2015). According to the MDG 2012 report, while

7
many regions worldwide were on track toward reaching the MDGs by the 2015 expected
target, most SSA nations could not (United Nations, 2012). The implementation and
achievement of the MDG in SSA encompass variabilities across national, sub-regional,
and sub-national units. National variations in achievement often reflect the baseline
disparities, while sub-national variations are associated with gender, socio-economical,
and geographic disparities in outcomes. Finally, in 2015, a new Sustainable Development
Agenda (SDA) and new goals were designed for 2030 at the UN summit (Adebowale et
al., 2017; Angoua et al., 2018). However, as Darvesh et al. (2017) repeatedly noted,
despite progress to minimize diarrhea-related mortality, the reduction in death and
incidence has varied and unequally distributed based on SES and region types. According
to the authors, various WaSH interventions have shown about 27% - 53% on diarrhea risk
reduction in children less than 5, depending on the intervention type. Therefore, the
authors suggested further evidence to support the scale-up of WaSH in these countries.
No studies that have addressed the current case of Cote D’Ivoire’s women and
their children as it related to the impact of WaSH on the mortality of children under 5
were found. This study examined the strength of the relationship between WaSH and the
under- 5 mortality of the target population. This study may add insight to the current
knowledge on the mortality of children less than 5 with regards to WaSH problematic.
The findings of this study may help improve programs to reduce childhood mortality and
morbidity and strengthen policies and practices to improve child survival in these
settings.

8
Problem Statement
According to the World Health Organization (WHO, 2021), about 5.2 million
children below 5 died in 2019, with 14,000 dying each day. When the probability of a
child dying between birth and age 5 is expressed per 1,000 live births, the rate is known
as the U5MR (UNICEF, 2019 c). In the WHO African Regions, U5MR was 76.5 per
1,000 live births in 2016, a rate that is almost eight times the risk in the WHO European
Region (WHO, 2018). Previous studies have shown a strong correlation between clean
water, adequate sanitation, child health, and survival (Alemu, 2017; Bohra et al., 2017;
Cairncross et al., 2010; Pink, 2013; World Health Organization, n.d.). The literature has
found diarrheal diseases among the leading cause of mortality for children in this age
range and suggested that the main route of transmission of these illnesses is associated
with improper sanitation, lack of potable water, and hygiene (Angoua et al., 2018; Clasen
et al., 2014; Darvesh et al., 2017; Pink, 2013; UNICEF Côte D’Ivoire, n. d.). According
to the United Nations Development Programme (2018), the scarcity of clean water and
basic sanitation services affects the lives of more than 40% of people worldwide.
Moreover, 61.1 million of the global disability-adjusted life-years (DALYs) are attributed
to unimproved water (95% UI 49.4 million to 69.6 million; 85.4% of diarrheal DALYs)
and 40.0 million DALYs (36.0 million to 44.4 million) to a lack of basic sanitation
services (Angoua et al., 2018). In fact, diarrheal diseases affect the lives of the most
vulnerable communities with lack or/and limitation of water and sanitation including
Cote D’Ivoire, a developing country located in West Africa and among the most affected
groups by this burden, are children under 5 (Angoua et al., 2018).

9
In Côte D’Ivoire, more than eight million individuals (about 43% of its
population) lack adequate sanitation sources, and more than four million still use unsafe
drinking water sources, particularly in rural areas (UNICEF Côte D’Ivoire, n.d.).
According to UNICEF, in Côte D’Ivoire, many children die every day from diarrhea and
other diseases associated with lack of water and adequate sanitation (UNICEF Côte
D'Ivoire, n. d). As an effective control strategy, many countries have implemented the
MDG water and sanitation program to address these public health issues by providing
people with access to clean and safe water and sanitation sources (United Nations, 2015).
The current MDG framework suggests that all countries should reduce their U5MR to no
more than 25 per 1,000 live births (WHO, 2018). Despite a remarkable global decline of
the U5MR by 56 percent, from 93 deaths per 1000 live births in 1990 to 41 deaths per
1000 live births in 2016; many countries (about 79 countries); particularly, SSA nations,
including Côte d’Ivoire, still lag behind with a much higher U5MR of 92 per 1,000 live
births in 2016 (The World Bank Group, 2018). For instance, the 2018 U5MR Sub
Saharan Africa is 78 per 1,000 live births as compared to 81 per 1,000 live births in 2018
for Cote D’Ivoire (The World Bank Group, 2019), which is far higher than the average
rate in the SSA regions.
Highlighted in Fink et al. 's (2011) article, the need to undertake more research to
support childhood survival programs and interventions aiming at reducing childhood
mortality. Even though a body of literature exists on the under-5 mortality research in
general, many of these studies mainly focused on the economic analysis of the investment
and its return about mortality/morbidity. Only few studies focused on morbidity and

10
mortality associated with WaSH burden (Cha et al., 2015; Clasen et al., 2014; Diouf et
al., 2014; Ezeh et al., 2014; Fink et al., 2011; Rasella, 2013). In Côte D’Ivoire, there is a
need to uncover to what extent the under-5 mortality is affected by WaSH and any other
associated exposure factors. The purpose of this study was to examine the magnitude of
the association between access to WaSH variables influencing the U5MR in Côte
D’Ivoire. This study tried to better understand the factors that affect the mortality among
children below 5 years of age. Further, the rationale of this study was that despite the
MDGs recommendations that all countries should reduce their U5MR to no more than 25
per 1,000 live births (WHO, 2018), the country has yet to do so. Cote d’Ivoire still lags
behind the expected target (e.g., 25 per 1,000 live births) with a huge U5MR of 92 per
1,000 live births in 2016 (The World Bank Group, 2018) and 81 per 1,000 live births in
2018 (The World Bank Group, 2019). A cross-sectional both descriptive and analytical
design was expected to explain the link between exposure and their predictive effect on
children under 5, using Cote D’Ivoire DHS data.
Purpose of the Study
The purpose of this study was to examine the magnitude of the association
between access to WaSH variables influencing the U5MR in Cote D’Ivoire. This study
focused on children under 5 because they are most affected by this problem associated
with limitation or lack of water/sanitation (Pink, 2013; Christophe et al., 2007; Cairncross
et al., 2010). This study used a quantitative paradigm, specifically a cross-sectional both
descriptive and analytical design, to analyze Cote D’Ivoire Demographic Health Surveys
(DHS) data sets containing the household questionnaires surveys data. Based on the

11
variables measurement levels, relevant statistical methods were used, including Cox
proportional hazards ratios to assess the magnitude of the relationship between variables
“access to improved water,” “improved sanitation sources,” and “hygiene” effect on the
“under-five mortality rates” in Cote D’Ivoire. “water,” “sanitation,” and “hygiene” were
the main predictors, and “under-five mortality rates” were the outcome variable in this
study. This research may contribute to the lives of the affected population while trying to
uncover the extent to which WaSH affects mortality in this age group.
Research Questions and Hypotheses
RQ1: To what extent does access to improved sanitation facilities affect the under-
5 mortality among women 15-49 in Cote D’Ivoire while controlling for
demographic, socioeconomic, and maternal variables?
H01: There is no statistically significant difference in the under-5 mortality while
controlling for demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved sanitation facilities and
those without.
HA1: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved sanitation facilities and
those without.
RQ2: To what extent does access to improved water sources affect the under-5
mortality among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables?

12
H02: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources and those
without.
HA2: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources and those
without.
RQ3: To what extent does adequate hygiene affect the under-5 mortality among
women 15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and
maternal variables?
H03: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with adequate hygiene and those without. HA3:
There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with adequate hygiene and those without.
RQ4: To what extent does access to improved water sources, improved sanitation
facilities, and adequate hygiene affect the under-5 mortality among women 15-49 in Cote
D’Ivoire while controlling for demographic, socioeconomic, and maternal variables?
H04: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among

13
women 15-49 in Cote D’Ivoire with access to improved water sources, improved
sanitation facilities, and adequate hygiene and those without.
HA4: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources, improved
sanitation facilities, and adequate hygiene and those without.
Conceptual Framework
The integrated behavioral model for water, sanitation, and hygiene (IBM-WASH)
and the health and human rights framework are the conceptual framework for this study.
Designed by Dreibelbis et al. (2013), the IBM-WaSH provides a practical and conceptual
tool for understanding and assessing multilevel and multidimensional determinants of
WaSH practices in infrastructure-stretched settings. The IBM-WaSH requires individual
behavioral outcomes that must be taken within the wider communal and societal context
where these occur. The focus of the IBM-WaSH model is on the formation of habits and
behaviors not explicitly on the reduction of exposure. Hence, this approach assumes that
improving WaSH practices will lead to a reduction of exposure to pathogens. The success
of intervention to improve WaSH practices relies on the ability to foster and maintain
behavior change at the individual, household, community, and structural levels.
The human right approach could explain the linkage between access to
sanitation/water and health outcome of the affected community. This perspective applied
to water and sanitation situations can enhance the health of the underserved population, in
addition to structural change pertaining to the social determinants of the health-

14
illnesscare process involved (Neves-Silva & Heller, 2016), and more specifically, the
morbidity and associated mortality of WaSH related burdens on children under 5. The
proposed combined framework will uncover a mix of the multiple levels of influence that
may shape behavioral-level outcomes, including the three intersecting dimensions that
influence WaSH behaviors (the psychological, the contextual, and the technological
dimension; Dreibelbis et al., 2013). One such perceived norm influences motivation to
comply and personal attitudes as determinants to various outcomes, such as consumption
of potable water and routine personal hygiene; thereby, their overall influence on under-5
mortality. Using this multilevel approach will provide insights on differential compliance
for preventive behaviors, self-efficacy, underlying beliefs to differential pathways,
outcomes norms, attitudes/behavior, beliefs, and intentions to adopt preventive measures
associated with WaSH and beyond. Overall, using the human health approach could
explain the linkage between access to sanitation/water and health outcome of the affected
community. This perspective applied to water and sanitation situations can enhance the
health of the underserved population as well as structural changes about the social
determinants of the health-illness-care process (Neves-Silva & Heller, 2016).
Nature of the Study
I conducted a quantitative study using an analytical cross-sectional study design.
This correlational scientific inquiry is relevant, as it does not intend to manipulate the
predictors and or assign the study participants to conditions as in experimental studies
(Sullivan, 2012). However, this design statistically explored and explained the
relationship between improved sanitation, water sources, and hygiene and their influence

15
on the under-5 death numerically and descriptively in addition to making inferences
based on estimates from the sample to the population (Crosby et al., 2006;
FrankfortNachmias & Nachmias, 2008; Szklo & Nieto, 2014).
Quantitative cross-sectional designs can rely on existing differences rather than
fluctuation due to interventional effect, in addition to the fact that the selection of groups
will depend on existing differences rather than random allocation, and no time dimension
is a concern (USC, 2013). As mentioned earlier, the present study used a cross-sectional
design for a secondary data analysis from Cote D’Ivoire pooled DHS by merging all
available datasets between 2005 and 2020 at the time of analysis. So, because the DHS
data are pre existing data with a known design (cross-sectional), users of such data are
already driven by the preexisting design set by the primary data collectors/researchers.
Based on the variable measurement levels, I used relevant statistical methods such as Cox
proportional hazards ratios to estimate the strength of the relationship between WaSH
(i.e., sanitation, water, and hygiene) as independent variables and potential confounders.
These included: household wealth index, mother literacy level, paternal level of
education, place of residence (urban versus rural), maternal education, mother
employment status, number of residents in the household over the age of 5, father work
status, presence of child health with the mother, child from a multiple birth, and religion,
as well as child age at birth, child gender/sex, mother age at childbirth, and perceived
newborn size at birth by mother (small or very small, and average or large). Lastly, the
level of U5MR was assessed as the outcome variable, while controlling for confounding
and interaction effects simultaneously.

16
Definitions
Ezeh et al. (2014) suggested the following definitions based on WHO/ UNICEF
guidelines, in this classification, both sanitation and water sources are classified as
improved versus unimproved, as seen in Table 1 (Ezeh et al., 2014; Yaya et al., 2018).
Sanitation: “The provision of facilities and services for safe management and
disposal of human urine and feces” (Pseau, 2016, p. 24).
Hygiene: “The conditions and practices that help maintain health and prevent the
spread of disease including handwashing, menstrual hygiene management, and food
hygiene” (Pseau, 2016, p. 24).
According to the CDC (2017), access to sanitation is measured by the percentage
of the population with access and using improved sanitation facilities.
Improved sanitation facilities usually ensure separation of human excreta from
human contact, and include the following:
● Flush or pour-flush toilet/latrine to:
o Piped sewer
system o Septic tank
o Pit latrine
● Ventilated improved pit (VIP) latrine
● Pit latrine with slab
● Composting toilet (CDC, 2017, p. 1).

17
Yaya et al. (2018) suggested almost similar definitions for improved sanitation facilities,
seen as pit latrines, flush/pour flush to the piped sewer system, septic tank, VIP latrine,
composting toilets, and pit latrine with slab (see Table 1).
Shared sanitation facilities are of an otherwise acceptable improved type of
sanitation facility that is shared between two or more households. Shared facilities
include public toilets.
Unimproved sanitation facilities do not ensure hygienic separation of human excreta
from human contact and include:
● Pit latrine without a slab or platform
● Hanging latrine
● Bucket latrine
● Open defecation in fields, forests, bushes, bodies of water or other open
spaces, or disposal of human feces with solid waste (CDC, 2017, p. 1)
Improved drinking-water sources include standpipes or public taps, protected
springs or rainwater collection, boreholes, tube wells, protected dug wells, or piped water
on-premises, which refers to piped household water connection located inside the user’s
dwelling, plot, or yard (Yaya et al., 2018; see Table 1).
Table 1.
Water and Sanitation Sources Classified by WHO/UNICEF Guidelines
Unimproved
Improved
18
Sanitation
Unimproved sanitation facilities do not
ensure hygienic separation of human
excreta from human contact. Unimproved
facilities include pit latrines without a slab or
platform, hanging latrines and bucket
latrines.
Improved sanitation facilities ensure hygienic
separation of human excreta from human contact.
They comprise of the following facilities: Flush/pour
flush to piped sewer system, septic tank, pit latrine;
ventilated improved pit (VIP) latrine, pit latrine with
slab, composting toilet.
Water
Unimproved drinking-water sources include
Unprotected dug well, unprotected spring,
cart with small tank/drum, surface water
(river, dam, lake, pond, stream, canal,
irrigation channels), and bottled water.
Improved drinking-water sources include public taps
or standpipes, tube wells or boreholes, protected dug
wells, protected springs, or rainwater collection. Piped
water on premises: Piped household water
connection located inside the user’s dwelling, plot, or
yard.
Source: (Yaya et al., 2018).
Educational level represents the number of years of education the participants
attained.
Socioeconomic status represents the annual income of the study participants.
Assumptions
In this research study, various assumptions were made to address the research
questions and hypotheses. I assumed that the DHS data are suitable for my study with
regards to the design, methodology, and instrumentation used. I also assumed that the
primary data’s quality (i.e., validity and reliability) has been already evaluated and
ensured in the full database and has all the variables and information needed for the
current study. I also assumed that the study participants have been able to understand the
meaning of the questions asked in the DHS questionnaires. Additionally, I assumed the
study respondents have fully completed the questionnaire with honesty, accuracy, and
integrity. However, I am aware that social desirability, selection bias, and recall bias may
have occurred. For instance, some respondents tended to consistently respond in certain
ways, whether positively or negatively, or with inaccurate information due to memory

19
lapse or recall. I also assumed that data collectors have addressed sampling biases with
relevant sampling designs. Moreover, I assumed that these data were already prepared to
generate available and ready-to-use survey designs and weights variables - something
that many data users may not be able to do, yet this helps data users to make needed
adjustments to their estimates (Cheng & Phillips, 2014).
Scope and Delimitations
The delimitations of this research include the age range, being child-bearer or
caregiver /mother with children under 5 years old and residing in a household located in
Cote D’Ivoire at the time of the surveys. This study used pooled Cote D’Ivoire DHS
household surveys data including women of all ethnicities who strictly were considered
to be of reproductive age, ranging between 15 and 49 years old, who were living in Cote
D’Ivoire at the time of the surveys. Therefore, all the remaining people, both male and
female aged under 15 years and more than 49 years, were excluded in this research.
Given that many ethnicities were considered, the study results did not privilege one
ethnicity over another. Moreover, to meet the inclusion criteria, women must be between
15 and 49 years, as such age group is within the reproductive age and must be residents
of Cote D’Ivoire.
Limitations
Doolan et al. (2009) suggested that researchers interested in secondary data
analysis must understand the concepts of research with regards to designing a new study,
but also must be aware of challenges specific to conduct research using an existing data

20
set. There is a huge amount of existing data, and many of them use cross-sectional
designs such as huge population-based surveys (i.e., DHS data), the source of my
selected data. According to Oxbridge Essay (n.d.), several limitations can challenge the
use of secondary data regardless of the designs applied in these studies. These include a)
the data inappropriateness for the research purposes; b) the data format may not be as
expected; c) possible lack of validity and reliability of that data; d) the data may not be
suitable for the new research question; and e) lack of sufficient information about their
research (Oxbridge Essay, n.d.), not only data can be gathered inaccurately, but also some
data can be missing.
Fortunately, the DHS data, a well-recognized data set, has been cleaned by
professionals and provides detailed documentation regarding the data collection and
cleaning process. It has a relatively high quality (both validity and reliability). In fact, a
major challenge when dealing with secondary data including the DHS data is the fact that
the data is already there with a specific form that cannot be changed, the rest is to be able
to develop the research question to match with the data as well as the proper data analysis
to address the research question(s) (Laureate Education, Inc., 2013c). According to
Doolan et al. (2009), the challenge led by the fact that secondary data sets have been
collected based on other research question(s) with different measurement strategies and
methods that are not always what the present study using them would have expected, is
limiting.
One essential challenge associated with cross-sectional research using secondary
data is the fact that this data has been already captured at one point in time; thus, the

21
relationship between variables at that time (where data were collected) can fluctuate.
Therefore, in such design (cross-sectional), one could miss potential or occurring
relationships that may arise over time. In addition, only correlations can be assessed, no
causal link can be ascertained in cross-sectional design including this study, unless
further studies are conducted to assess causality between the study variables. A
crosssectional design cannot ascertain a spatiotemporal linkage between exposure-health
outcome sequence (Aschengrau & Seage, 2014; Gordis, 2009; Moeller, 2011; Szklo et
al., 2014).
Another limitation with secondary research in general, is that unlike in primary
research where the researcher controls both the design and the implementation of the
study. Having control of all the scientific protocol that is relevant for effective research.
The researcher will make a choice based on his expertise, interest, purpose/objective, the
research question, hypotheses, as well as the problem they want to solve in a specific
target population. In contrast, in secondary research like what I undertook, this freedom is
challenged by the fact that the data are already collected in a specific population (Côte
D’Ivoire, DHS data) and I was not involved in that process. Hence, this process was done
with a previously selected sampling strategy and research design associated with the type
of study the primary investigators have planned. Therefore, as a secondary researcher
using the DHS data, I do not have control over the study design prior to frame the
research questions of my study. Not being involved in that early stage of the study
implementation to data collection, I may have missed any nuances in the data collection
process that might help in the interpretation of results, as Cheng et al. (2014) pointed out.

22
Significance of the Study
WaSH related burden e.g., high U5MR, is an issue of great public health
significance. This study is essential, as it will address a critical social problem, namely
under 5 mortalities. This study is also significant because it examined how WaSH and
other covariates (considered in this study as confounders/effect modifiers) influence
U5MR; most essentially, public health officers, program planners, and government
agencies may get a better understanding of this problem and its impact on the affected
population’s wellbeing, health, and survival. Water and sanitation-related burden
threatens the lives of millions of people around the world, mainly children (Pink, 2013).
Each year, 10 million children under 5 years old with about 90% of them reside in 42 of
this, about 36 are in SSA (Fotso et al., 2007), including Côte D’Ivoire. In fact, 85% of
diseases associated with water supply are induced through oral transmission, mainly
diarrhea which leads to mortality in children (Cairncross et al., 2010). Also, diarrhea is
still the main cause of mortality among children under 5 (Fotso et al., 2007; UNICEF,
2019b). Moreover, as the main cause of death for children in this age range, diarrhea
(Fotso et al., 2007) has transmission pathways that are mostly linked to improper
sanitation and lack of potable water (World Health Organization, n. d.) and hygiene.
Furthermore, about 90% of the decline in diarrhea and a reduction of 2.2 million in
mortality rate were achieved through the provision and access to potable water and
proper sanitation (Pink, 2013).
Given the public health significance of WaSH-related mortality, the MDG has
proposed strategies to tackle this problem by providing improved sanitation, potable

23
water, and hygiene education to the priority population (United Nations, 2015). The
current MDG framework suggests that all countries should reduce their U5MR to no
more than 25 per 1,000 live births (WHO, 2018). However, Cote d’Ivoire is still lagging
the expected target (about 25 per 1,000 live births) with a higher U5MR of 92 per 1,000
live births in 2016 (The World Bank Group, 2018). To better understand the factors that
affect the high mortality rates of the children under 5 in this country, a cross-sectional
analytical design may examine all factors simultaneously in addition to WaSH variables
as determinants to children survival using the DHS data.
The insights derived from this study may lead to positive social changes by
providing public health professionals, program planners, and governmental agencies
involved in children health, an additional insight and understanding of the issue of WaSH
and related morbidity and mortality. Using this evidence, interested stakeholders could
design interventions/programs that take into consideration all the risk factors associated
with mortality in children under 5. Furthermore, the information gathered from this study
may help or guide these interested stakeholders in decision making pertaining to steps to
be taken to influence societies’ behaviors and attitudes for better health outcomes.
Assessing and understanding the current magnitude of the WaSH effect on the
under-5 mortality may contribute to reducing associated preventable morbidity and
mortality. The positive social change implications for the results of the study may be to
provide tangible and substantial evidence that would not only inform decision making for
further planning purpose, but also help to design effective upstream population-based
strategies (i.e., health education, improvement of quality of life, well-being, and survival

24
overall) to mitigate the health burden of the affected population in Cote D’Ivoire and
beyond. Using evidence from this study, public health practitioners, researchers, program
planners, and funders could make informed decisions to improve the program, advocate
more resources for the program, and help the affected communities in Cote D’Ivoire and
other regions in need of similar interventions. Lastly, the overall outcome would be to
empower the community in terms of improving their quality of life, well-being, and
associated mortality and morbidity. This, in turn, would impact life expectancy, the
WaSH program sustainability, advocacy needs, and survival (Parker & Thorson, 2009).
Summary and Transition
As aforementioned, this secondary analysis focused on women and their children
under 5 in Cote D’Ivoire, West Africa, facing premature death associated with limitations
in basic needs such as clean water, adequate sanitation, and hygiene. The finding of this
research may lead to positive social changes with an in-depth understanding of how
WaSH and covariates influence U5MR in Cote D’Ivoire by providing program planners,
public health practitioners, and governmental agencies important insights on how to
design more effective strategies and programs to address the problems faced by the target
population. I described the background for the study with a brief literature review to
support WaSH and confounding factors which may influence the health and mortality of
children less than 5. I also incorporated the research questions, the problem statement, the
conceptual framework, definitions of terms, the purpose of the study, the nature of the
study, significance, assumptions, scope and delimitations, and summary.

25
In Chapter 2, I provide a holistic review of available literature that summarizes
the body of knowledge on WaSH and its impact on the mortality of children under 5,
other risk factors, and associated morbidity. I also discuss the conceptual framework, the
methods used to conduct the literature review, the literature review related to key
variables and/or concepts, the justification derived from the literature and rationale to
study WaSH, other contributing risk factors associated with the U5MR, and the
relationship of WaSH and child morbidity and mortality.
Chapter 2: Literature Review
According to the WHO (2019), “5.6 million children under age five died in 2016,
15,000 every day” (para 1). In the WHO African Regions, the U5MR was 76.5 per 1,000
live births in 2016, which is almost eight times the rate in the WHO European Region
(WHO, 2019). Previous studies have shown a correlation between clean water, adequate
sanitation, child health, and survival (Alemu, 2017; Bohra et al., 2017; Cairncross et al.,
2010; Pink, 2013; World Health Organization, n. d.). Some of these literatures have
identified diarrheal illnesses among leading risk factors for death among children below 5
and suggested that the main route of transmission of these illnesses is associated with
improper sanitation, lack of potable water, and hygiene. According to the United Nations
Development Programme (2019), the scarcity of clean water and basic sanitation services
affect the lives of more than 40% of people worldwide. Moreover, unimproved water
conditions alone accounted for 61.1 million of the global DALYs with 95% UI 49.4
million to 69.6 million, 85.4% of diarrheal DALYs. Lack of sanitation services alone

26
accounted for roughly 40 million DALYs (36.0 - 44.4 million; Angoua et al., 2018). In
fact, diarrheal diseases affect the life of the most vulnerable communities with lack
or/and limitation of water and sanitation sources, including the population of Cote
D’Ivoire. Among the most affected groups by this burden are children under 5 (Angoua et
al., 2018). Yet, despite a remarkable global decline of the U5MR by 56%, from 93 deaths
per 1.000 live births in 1990 to 41 deaths per 1,000 live births in 2016, about 79
countries, particularly SSA countries including Cote d’Ivoire, still lag behind with a
much higher U5MR of 92 per 1,000 live births in 2016 (The World Bank Group, 2018).
Only a few studies focused on morbidity associated with WaSH burden (Cha et al., 2015;
Clasen et al., 2014; Diouf et al., 2014; Ezeh et al., 2014; Fink et al., 2011; Rasella, 2013).
The current study explored the magnitude of the association between access to
WaSH and the under 5 mortality rates in Cote D’Ivoire. This research used a quantitative
paradigm, specifically, a cross-sectional analytical design to analyze Cote D’Ivoire DHS
data sets containing the household questionnaires survey data. The following sections
will be discussed:
● Methods used to conduct the literature review
● Conceptual framework
● Literature review related to key variables and/or concepts
● Justification derived from the literature and rationale to study WaSH and other
contributing risk factors associated with the U5MR
● The relationship of WaSH and child morbidity and mortality
● Studies about diarrhea-related burden and other covariates of WaSH.

27
Literature Search Strategy
The literature was searched using the following databases: MEDLINE, CINAHL,
EBSCO, PubMed, Web of Medicine, Lancet, Science Direct, Sage, and ProQuest
Dissertations & Theses Global. The keywords used for the literature search included:
“water”; “water AND under-five mortality ”; “water AND sanitation”; “water, sanitation
AND hygiene”, “ access to improved water and sanitation sources ”; and “access to
improved water, sanitation, hygiene, AND under-five mortality”. Papers published since
2014, in English, online and peer-reviewed journals, as well as textbooks and Walden
materials, were included in this review. Papers about treatments and laboratory-based
basic science were excluded. The basic key search terms are the following: water,
sanitation, hygiene, under-five, water, sanitation, and hygiene-related child mortality,
west Africa, Côte d’Ivoire, and risk factors associated with under 5 mortality rates among
children in Cote D’Ivoire.
Conceptual Framework Overview and Research Related to WaSH
Theories, research, and practices are applied to understand the determinants of
behaviors, evaluate change strategies, and convey effective interventions (Glanz &
Bishop, 2010). To address WaSH related health issues e.g., mortality among the under 5
subgroups, a combination of multiple elements must be taken into consideration context
based. This is because our health outcomes have multifactorial determinants (Schneider,
2011; Wilkinson & Pickett, 2010).Thus, integrating various theories/concepts aligned
with a relevant system thinking approach into a comprehensive model, encompassing an

28
insight of the elements of each theory and other approaches, may help compensate for
limitations of each individual theory in addition to uncover salient underlying
determinants of child health outcomes. As mentioned in the previous section, the
IBMWaSH and the health and human rights approach for water and sanitation would be
used in this study.
According to the Human Rights Councils:
The human right to safe drinking water and sanitation is derived from the right to
an adequate standard of living and inextricably related to the right to the highest
attainable standard of physical and mental health, as well as the right to life and
human dignity. (United Nations Human Rights, n.d., p. 2)
Initially established in 1977 in Argentina during the United Nations Conference
on Water, the human right framework was advocated by earlier pioneers including
Jonathan Mann. He suggested that the human rights framework provides a more useful
approach to tackle public health challenges than other traditional biomedical references
(Neves-Silva et al., 2018). At first, the United Nations General Assembly (UNGA) denied
the human right for water and sanitation (HRtWS) in 2008. Then, two years after it was
recognized (United Nations General Assembly, 2010) in 2010, UNGA recognized the
HRtWS as vital for all humans (Neves-Silva & Heller, 2016). Access to water and
sanitation has been recognized by the United Nations as a human right, as it reflects the
fundamental nature of these basic needs in the life of everyone. Lack of access to
affordable, safe, and sufficient WaSH sources lead to a devastating effect on the dignity,
prosperity, and health of billions of individuals around the world, yet leading to
substantial consequences for people to realize other human rights (United Nations Water,

29
2020). The approach can also make structural changes about the social determinants
related to the health-illness-care process with principle based on the fact that water and
sanitation are basic needs that must be accessible to anyone (Neves-Silva & Heller,
2016). According to the human rights perspective, these services are seen not only as a
right for all people, but also as an obligation for the state (Neves-Silva et al., 2016).
Overall, using the human right approach could explain the linkage between access to
WaSH and the health outcome of the affected community. As Ness et al. (2009) pointed
out, sustainability in their development should ensure provision and accessibility to
vulnerable communities to strengthen their health. The human right normative approach
associated with water and sanitation comprised the following criteria: safety/quality;
accessibility; acceptability; availability; and affordability. Similar criteria are employed
for the human right to sanitation; for instance, the privacy and dignity were applied and
tallied with people’s cultural and social standards and gender-related specificities with
regards to girls and women (Neves-Silva et al., 2016). The human right perspective
applied to the WaSH problem can enhance the health of the underserved disadvantaged
population.
IBM-WaSH is a synthesis of behavioral models associated with WaSH and
organizes factors affecting behavior in an ecological framework (Hulland et al., 2013).
According to Hulland et al. (2013), this model encompasses three dimensions including:
contextual factors (i.e., access to water and soap), psychosocial factors (i.e., perceived
risk of disease, disgust associated with contact with unclean objects, and pre-existing
habit), and technological factors (i.e., related to the physical hardware storing soap and

30
water), each of which function at five aggregate levels: interpersonal/household, habitual,
societal, individual, and community/structural. IBM-WaSH can help assess behavior
change programs and interventions in infrastructure-stretched settings. It contains various
behaviors that change concepts and theories to provide a simple and adaptive tool to
understand the formation of behavior and WaSH habits.
The IBM-WaSH Approach
The IBM-WaSH model synthesized previous behavioral models as a matrix
containing dimensions (three) and levels (five), aligned with the ecological model as
displayed below in Table 2.
Table 2.
The IBM-WaSH Matrix
Levels
Contextual factors
Psychosocial factors
Technology factors
Societal/Structural
Policy and regulations, climate,
and geography.
Leadership/advocacy,
cultural identity
Manufacturing, financing, and
distribution of the product;
current and past national
policies and promotion of
products
Community
Access to markets, access to
resources, built and physical
environment
Shared values, collective
efficacy, social integration,
stigma
Location, access, availability,
individual vs. collective
ownership/access, and
maintenance of the product
Interpersonal/Household
Roles and responsibilities,
household structure, division of
labor, available space
Injunctive norms,
descriptive norms,
aspirations, shame,
nurture
Sharing of access to product,
modeling/demonstration of
use of product
Individual
Wealth, age, education, gender,
livelihoods/employment
Self-efficacy, knowledge,
disgust, perceived threat
Perceived cost, value,
convenience, and other
strengths and weaknesses of
the product

31
Habitual
Favorable environment for habit
formation, opportunity for and
barriers to repetition of behavior
Existing water and
sanitation habits, outcome
expectations
Ease/Effectiveness of routine
use of product
Source: Dreibelbis et al., 2013.
The IBM-WaSH model includes three dimensions that intersect and affect WaSH constructs:
the psychological dimension, the contextual dimension, and the technological dimension (Dreibelbis
et al., 2013). According to the authors, the contextual dimension encompasses factors linked to the
individual, environment, and/or the setting that may affect fluctuations in behavior and the use of
novel technologies. The psychosocial dimension includes the psychological, the behavioral, or the
social determinants of technology adaptation and behavioral outcomes. The technological dimension
implies devices or products that affect its adoption and sustained use. These dimensions interact
together (i.e., contextual, technological, and psychological) and resonate with the concept of
reciprocal determinism in social cognitive theory, which describe reciprocal interactions between the
behavior, the environment, and the individual in which the behavior occurred (Bandura,1987). In
addition, the authors suggested five aggregate levels:
1. The societal/structural level represents the broad cultural, organizational, or
institutional factors that impact behaviors in each of the three dimensions e.g.,
geography, manufacturing, laws, policies, commercial, geology, and climate
(Dreibelbis et al., 2013).
2. The community level includes the social and the physical settings where
people reside and the institutions that govern societal behaviors and
experiences.

32
3. The interpersonal/household level encompasses both the people and the
individuals they interact with e.g., close friends, members in their households,
and neighbors. Factors implicated in this level include behaviors modeling;
shame; roles and responsibilities; aspirations; household wealth; descriptive
and injunctive norms; and sharing access to a product.
4. The individual level encompasses sociodemographic characteristics e.g.,
cognitive, gender, age, attitudes toward the product, behavior, or hardware.
5. The habitual level is the individual habits daily built repeatedly from the
opportunity and necessity attached to WaSH behaviors and several influencing
factors (Dreibelbis et al., 2013).
Most existing models in the literature tended to focus more on the individual level
factors of the behavior, rather than a wider ecological model view that positions
individual behaviors within a multi-level causal framework. However, others using a
multi-level approach are restricted to the psychological-related determinants of behavior.
For example, Rainey and Harding’s (2005) work using the health belief model in Nepal
to solar disinfection, explained how structural factors e.g., agricultural work and gender
roles limit women's commitment to household water treatment. WaSH behaviors, e. g,
steps to follow, when/where these behaviors must be undertaken for expected health
impact, as well as factors that influence the behavior to become a habit were scarcely
considered in the existing framework. However, the habit itself is an essential element for
WaSH practices. Improved WaSH practices are far from one-time behavior changes, as
they require substantial repetition across both space and time (Dreibelbis et al., 2013).

33
For instance, Jenkins and Scott (2007) and Wood et al. 's (2012) frameworks are used as
models to guide decision making to adopt specific technologies, unlike Wood et al.’s
models, which explicitly tackled factors associated with continued and sustained usage of
technology and its maintenance.
Literature Review The Link Between IBM-WaSH, the Human Right Approach, and
Health Outcome for the Under 5
The multiple levels dimension of the IBM-WaSH framework requires that any
individual behavioral outcome must be considered within the broader communal and
societal context in which it occurs. The IBM-WaSH model focuses on the formation of
habits and behaviors not explicitly on the reduction of exposure. Hence, this approach
presumes that improving WaSH practices may reduce exposure to pathogens. Yet it is
critical to have a better understanding of these behaviors’ determinants independent of
their direct linkage with transmission pathways (Dreibelbis et al., 2013). The success of
intervention to improve WaSH practices relies on the ability to foster and maintain
behavior change at the community, individual, household, and structural levels. As
mentioned earlier, the human right approach to WaSH and IBM-WaSH were used in this
study. The human right approach could explain the linkage between access to
sanitation/water and health outcome of the affected community. This perspective applied
to the water and sanitation situation can enhance the health of the underserved
population, as well as structural changes about the social determinants of the
healthillness-care process (Neves-Silva & Heller, 2016). Most specifically, the morbidity
and mortality of WaSH related burden on children under 5. The proposed combined

34
framework will uncover a mixed of the multiple levels of influence that may drive
behavioral related outcomes, including the three intersecting dimensions that influence
WaSH behaviors (i.e., technological, psychological, and contextual; Dreibelbis et al.,
2013). One such perceived norm influences motivation to comply and personal attitudes
as determinants to various outcomes, such as consumption of potable water and routine
personal hygiene. Thereby, their overall influence on under-five mortality. Using this
multilevel approach will provide insights on differential compliance for preventive
behaviors, self-efficacy, underlying beliefs to differential pathways, outcomes norms,
attitudes/behavior, beliefs, and intentions to adopt preventive measures associated with
WaSH and beyond. The following section encompasses the review of key variables and
concepts.
Literature Review Related to Key Variables and/or Concepts Under-5 Mortality
When the probability of a child dying between birth and age 5 is expressed per
1,000 live births, the rate is known as the under-five mortality rate (U5MR) (UNICEF,
2019 c). The Under 5 Mortality is an important indicator to evaluate the performance of a
country's health system (Pedersen, Liu, & Child Mortality Estimation, 2012).
Policymakers and health professionals have prioritized childhood health outcomes to
combat the increasing childhood mortality rates (Adebowale et al., 2017). By doing so
has prompted the creation of strategies to reduce childhood death by 2/3 among children
less than five between 1990 – 2015, based upon the Millennium Development Goals.

35
A Brief Overview of the MDGs, the Sustainable Development Goals (SDGs), and
WaSH
In 2015, it was estimated that 133 out of the 195 nations that have adopted the
MDGs failed to meet the expected target of a 2/3 reduction in U5MR (Adebowale et al.,
2017). Then the United Nations adopted the SDGs to ensure healthy lives and children's
well-being. For instance, the “goal 3 target 3.2” is to stop preventable death in children
(i.e., less than five years and newborns) by 2030 (Adebowale et al., 2017). The MDGs
were adopted in 2000 and since 2001 time-bound targets for various components of
development policy were set. The sanitation and drinking water targets were adopted in
2006, classified as Target 7C: “to halve the proportion of the population with no
sustainable access to safe drinking water and basic sanitation between 1990 and 2015”
(Bartram et al., p. 2). The SDA was developed in 2015 with new goals designed and
recommended for 2030. SDG 6 focuses on water-related issues (Pseau, 2016) with eight
targets such as achieving universal access sanitation, water, and hygiene services: and
protecting water resources and water-related ecosystems (Pseau, 2016). The main
difference between the old MDGs and the SDGs is that the SDGs focuses on
sustainability, while the SDGs address sustainable development in its multiple forms e.g.,
economic growth, social inclusion, and environmental protection (UN, 2015); “the
MDGs primarily focused on social issues”(Pseau, 2016, p.15). As Pseau (2016) pointed
out, the SDGs are to be achieved in line with the implementation of this agreement. SDG
6: “Ensure availability and sustainable management of water and sanitation for all”
(p.13).

36
As mentioned in the early section, the concepts of WaSH initiatives reflect good
hygiene practice, access to improved sanitation, and water sources, critical to minimize
environmental health risks for the wellbeing and health of the population worldwide
(Angoua et al., 2018). Based on WHO/UNICEF guidelines, Ezeh and associates defined
improved water and improved sanitation. Like Ezeh et al. (2014) and Yaya et al. (2018),
Bartram, Brocklehurst, Fisher, Luyendijk, Hossain, Wardlaw, and Gordon (2014)
described the measurement method used by WHO/UNICEF to classify WaSH quality and
access. The authors used DHS household surveys and linear regression modeling for their
analysis. Below, I will discuss the evidence-based literature that supports this study.
Justification Derived from the Literature and Rationale to Study, WaSH, and
U5MR
WaSH and Associated Burdens
As mentioned in previous sections, water and sanitation-related-burden threaten
the lives of millions of people around the world, mainly children (Pink, 2013). Yet
annually there are about 10 million children less than 5 years old with about 90 % of
them residing in forty-two nations of this, thirty-six from SSA (Fotso et al., 2007)
including Côte D’Ivoire. According to Adebowale et al. (2017), the U5MR is highest in
SSA with 1/12 deaths during the first 6 months of SSA child, 12 times more than the 1/
147 in developed nations. About 85% of diseases associated with water supply are
induced through oral transmission, mainly diarrhea which leads to mortality in children
(Cairncross et al., 2010). As mentioned in the introduction, there is a linkage between

37
diarrheal diseases, WaSH, child morbidity, and mortality. Diarrhea remains the main risk
factor of death in children below age five (Darvesh et al. ,2017; Fotso et al., 2007). Its
transmission pathways are mostly associated with improper sanitation and lack of potable
water (Angoua et al., 2018; Pink, 2013; World Health Organization, n. d); as well as poor
hygiene. Some studies have revealed that about 90% of the decline in diarrhea and a
reduction of 2.2 million in mortality rate were achieved through the provision and access
to potable water and proper sanitation (Pink, 2013). For instance, various WaSH
interventions indicated a reduction of risk for between 27% and 53% in children less than
5 years old depending on the type of intervention used (Darvesh et al., 2017). Finally, the
authors suggested further research must be undertaken to evaluate these interventions'
impacts in different contexts. This approach is also supported by many authors including
Alemu et al (2017) and Angoua et al (2018). From Gorham and associates' (2017) view,
diarrheal illnesses are the underlying cause of death for approximately1.5 million people
globally in 2012. About 502,000 annual deaths are attributed to poor WaSH conditions in
low/middle-income countries; this represents more than half (58 percent) of cases-
specific related deaths (Gorham et al., 2017).
Factors Explaining the High Mortality Rates in Africa Water and Sanitation
WHO/UNICEF suggested that poor sanitation and water cause about 28% of child
mortality and adequate water and sanitation sources were not only cost-effective , but
also proven interventions (Alemu, 2017). According to Alemu (2017), about 9 in 10
diarrheal incidence cases could be averted with proper water and sanitation use. The use
of proper toilets can drop incident diarrhea by approximately 40%. Moreover, proper

38
sanitation can substantially reduce the main risk factors for child death, including
pneumonia and undernutrition. Hence, tackling issues related to access to sanitation is
important to minimize the mortality rate by 2/3 in childhood (Alemu, 2017).
These paragraphs account for the disparity in socioeconomic status (SES);
geographic setting (rural versus urban; slums, war zones); the difference in access,
availability, and quality of WaSH; diarrhea diseases; other infectious diseases; and policy
implications. Several factors are implicated in the access and the differential outcomes of
WaSH related burdens. Given the new MDGs targets of SDGs, the interaction between
improvement in children's health and non-health fields have been increasingly
recognized. Hence, WaSH interventions (i.e., improvement of access to good WaSH) to
provide opportunities to enhance the well-being and health of children through preventive
actions such as improvement of their nutritional status and halting the transmission of
communicable illnesses (Darvesh et al., 2017). In convergence with this perspective,
Angoua et al. (2018) suggested that rural exodus, poor socioeconomic conditions, and
geographic settings predict access to water and sanitation (WS). As the authors pointed
out, people residing in poor peri-urban communities in SSA cities are still challenged by
access to WS.
Alemu (2017) expressed similar views regarding the differential level of access to
WS sources based on geographic setting comparing several African countries. From the
WHO/UNICEF (2012) assessment, progress made by Africa with regards to access to
basic sanitation is still low and limited. From 1990 to 2010, about 35-40 % increase in
access to sanitation was done with a gain of 189 million with access (Alemu, 2017). With

39
the huge population growth, the urban population has doubled between 1990 to 2010,
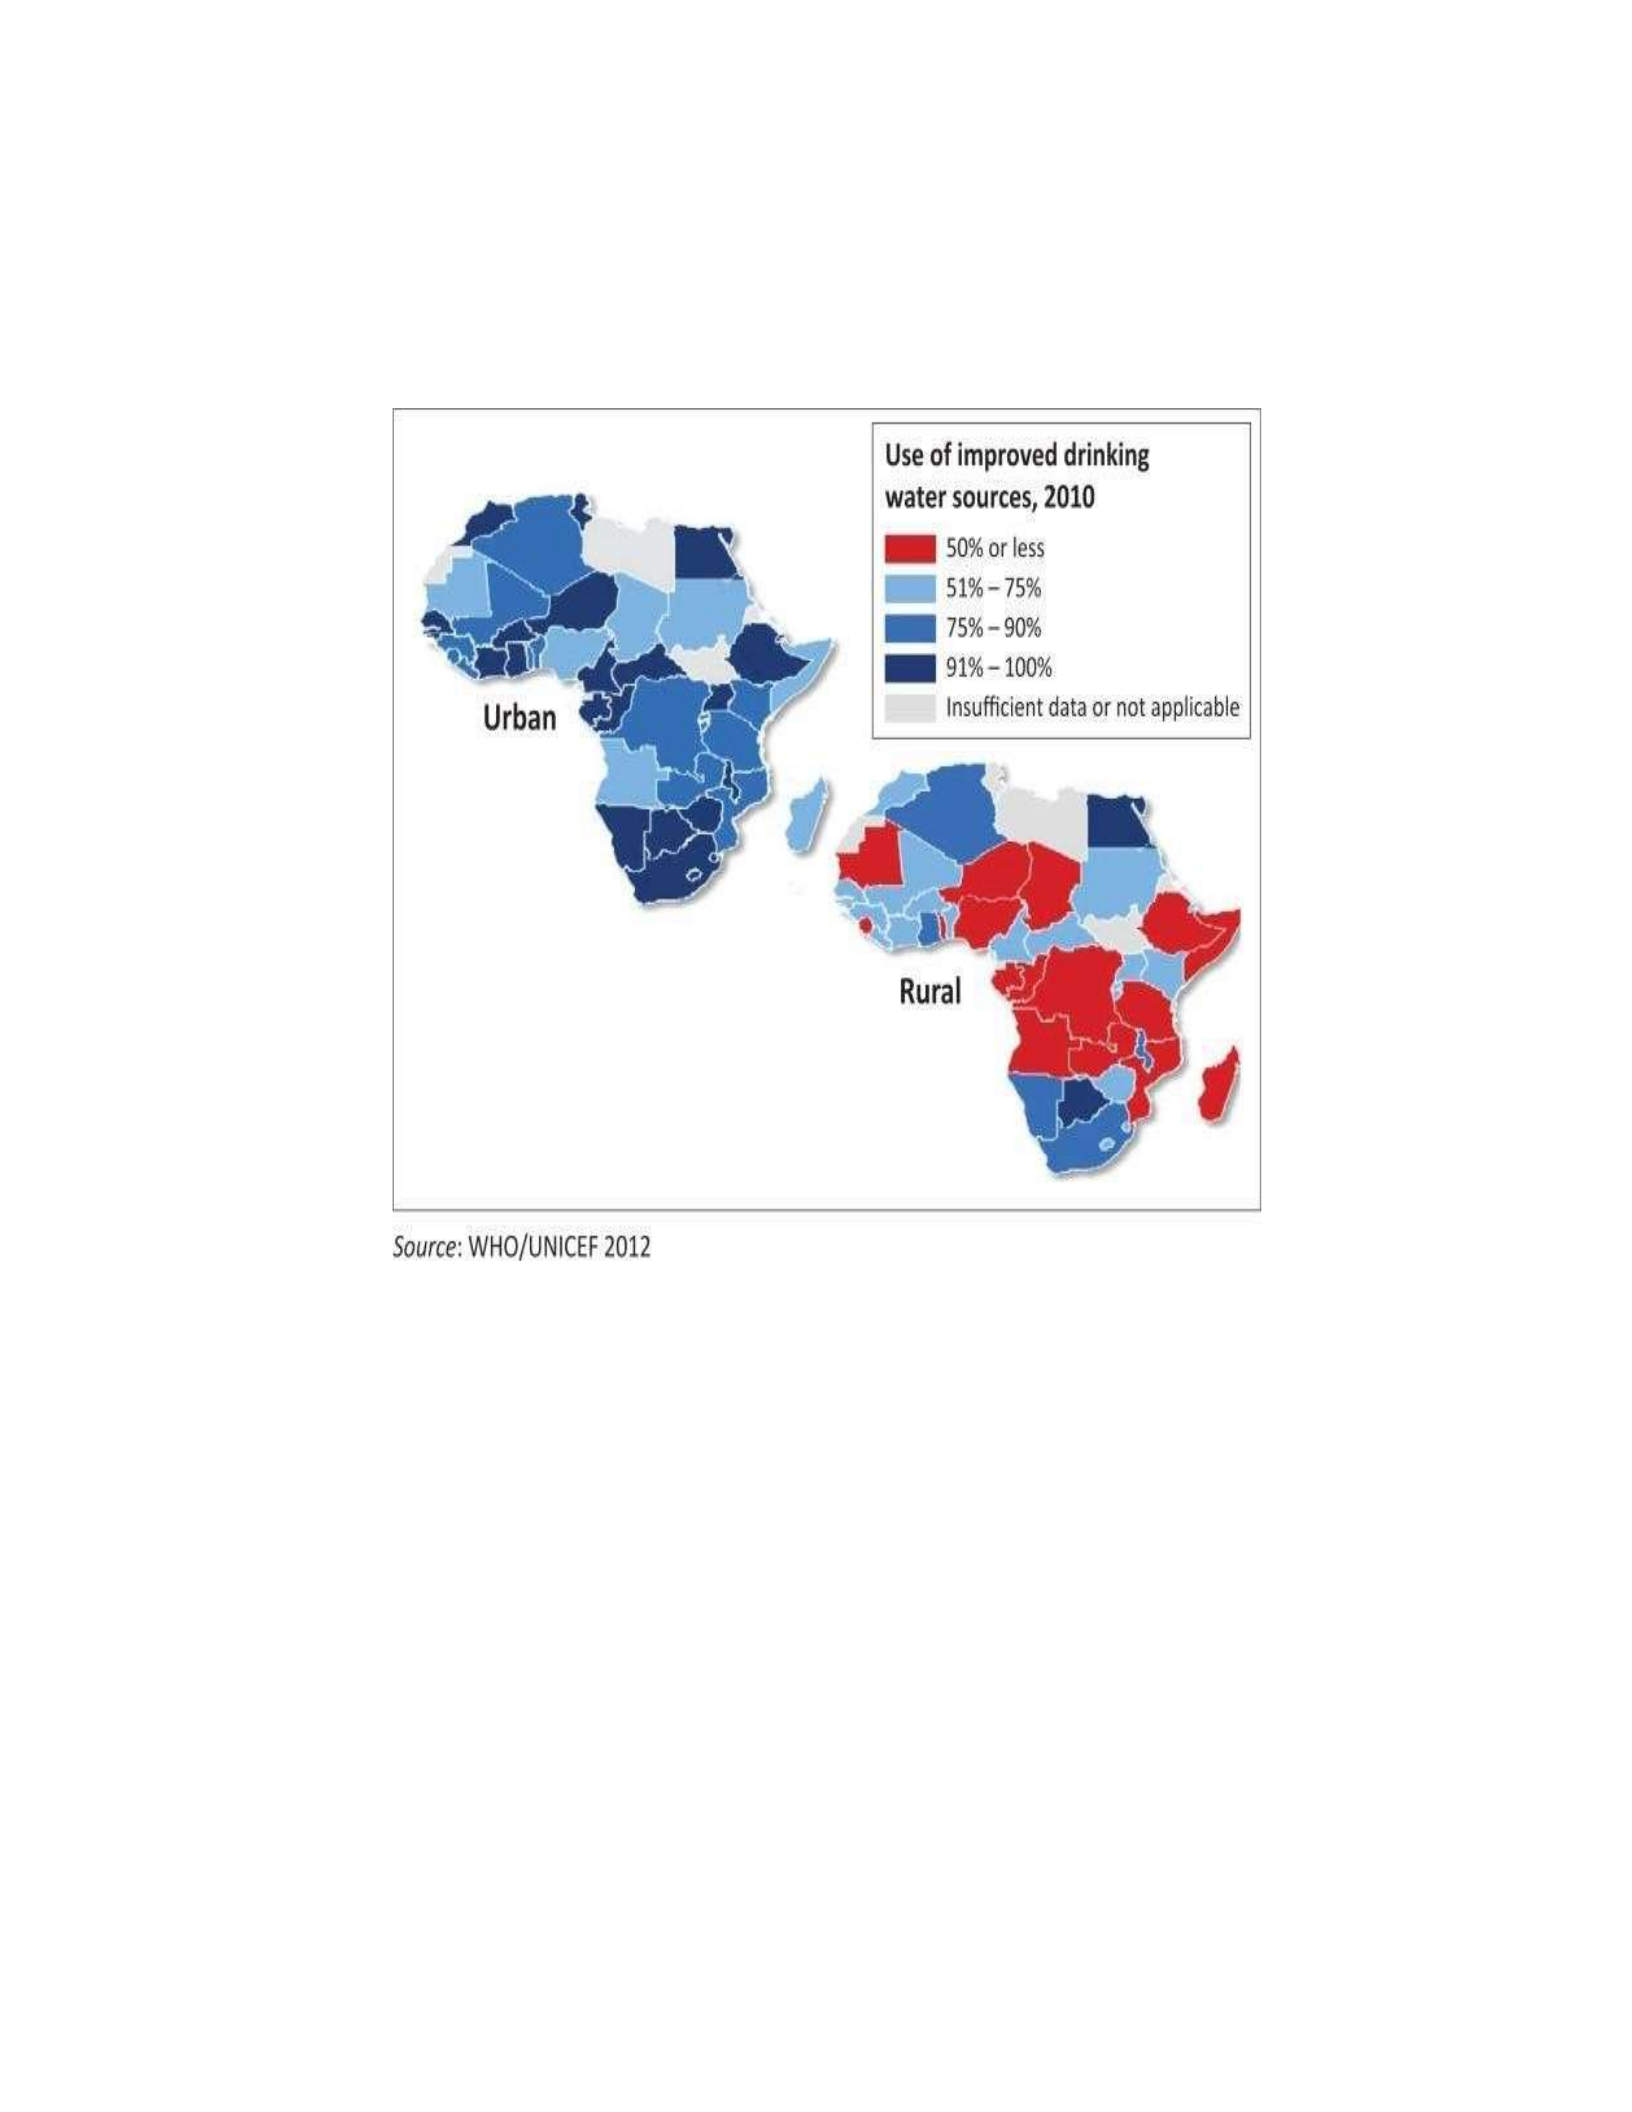
more than 1 out of 4 people rely on public or shared sanitation sources in urban zones. As
the author pointed out, in Africa, Egypt, Namibia, Botswana, and South Africa are the
only nations to achieve about 91 to 100 % coverage level of improved drinking water use
nationally. However, the most striking is the disparity between rural versus urban
populations with regards to access to WS. For instance, as Alemu noted , with a manifest
graphical display, despite having a higher population in almost all African nations, rural
settings are still lagging behind to get access to clean drinking water as shown in Figure 1
below (Alemu, 2017).
40
Figure 1
Use of Improved Drinking Water in Urban and Rural African Countries in 2010
Note. For more details see Alenu (2017). African Journal of Primary Health Care &
Family Medicine, 9(1), 1370. http://doi.org/10.4102/phcfm.v9i1.1370.
The Link Between the Use of Sanitation in Selected African Countries and IMR,
Under 5 Years Old in 2010
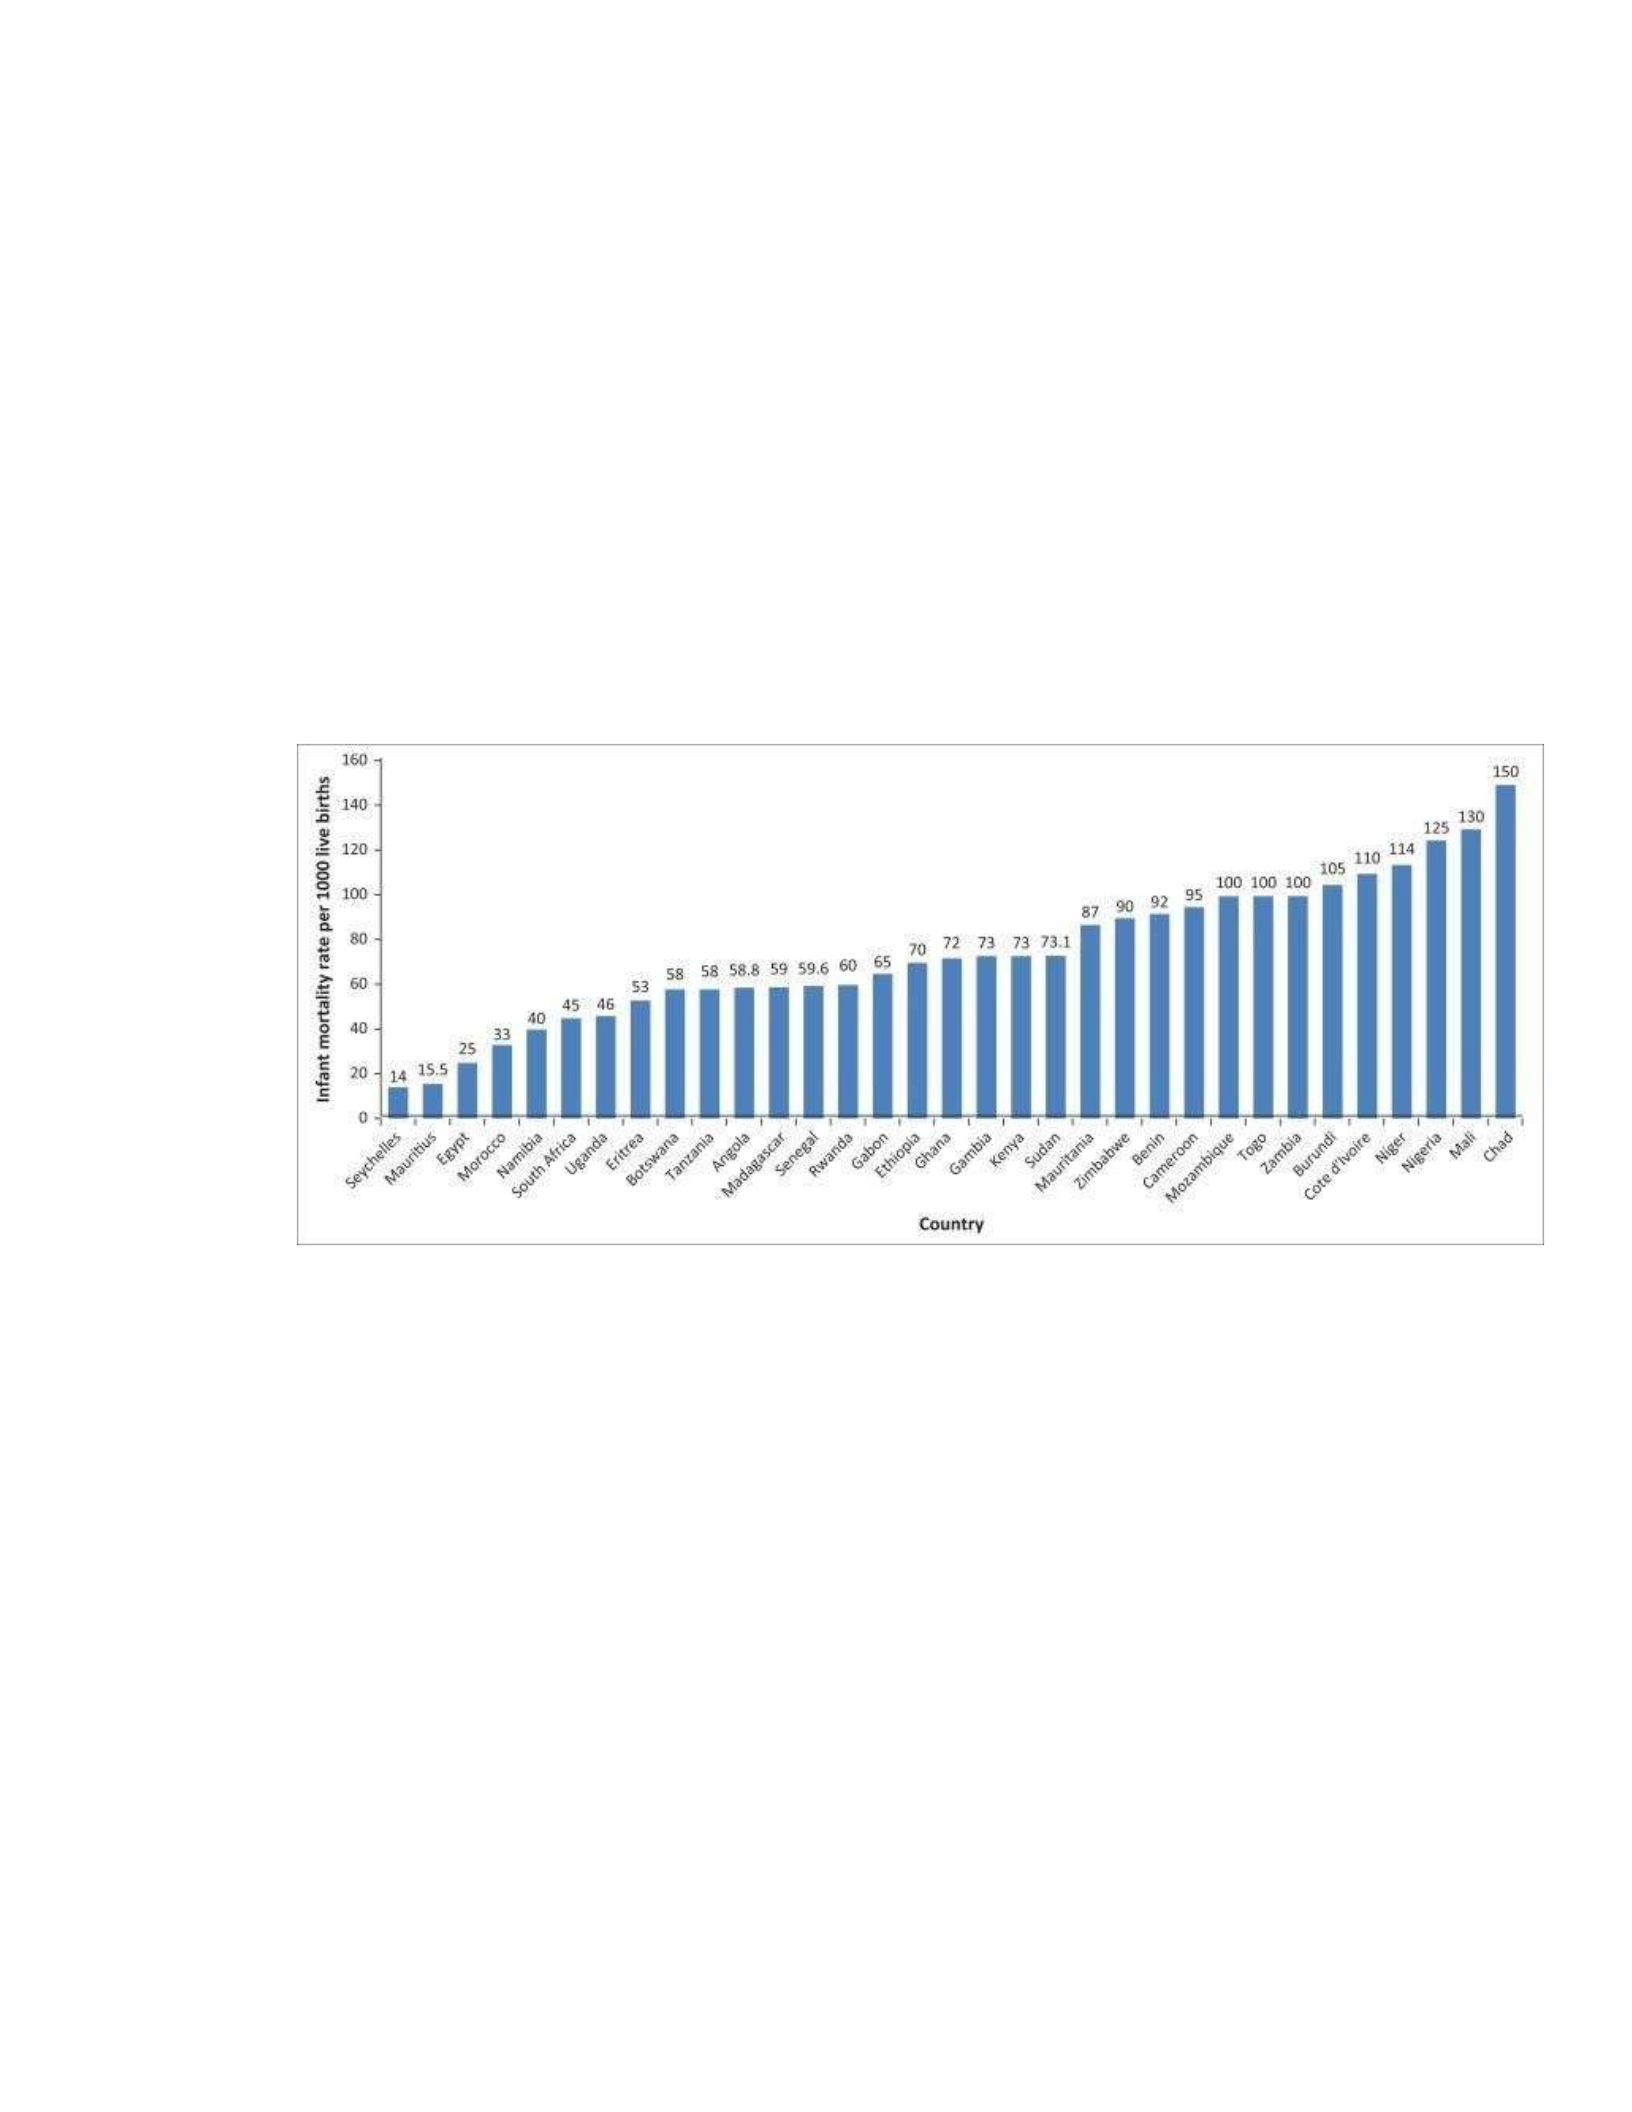
In Figure 2 and 3, Alemu (2017) compared the rates of child mortality per 1000
lives of birth and improved sanitation sources level in 2010 for about 33 African nations.
In Figure 2, Egypt, Namibia, Seychelles, Morocco, Mauritius, and South Africa are
41
classified as top nations with a substantial reduction of their IMR and U5MR. Seychelles,
for instance, IMR per 1000 live births is about 14, while in contrast, countries such as
Niger, Chad, Nigeria, Mali, Burundi, and Cote d’Ivoire have a higher IMR (Alemu,
2017).
Figure 2
Infant Mortality Rate per 1000 Lives of Births in Africa in 2010.
Source: Alemu (2017)
Link Between the Use of Improved Sanitation in Selected African Nations and IMR,
Under 5 Years Old in 2010
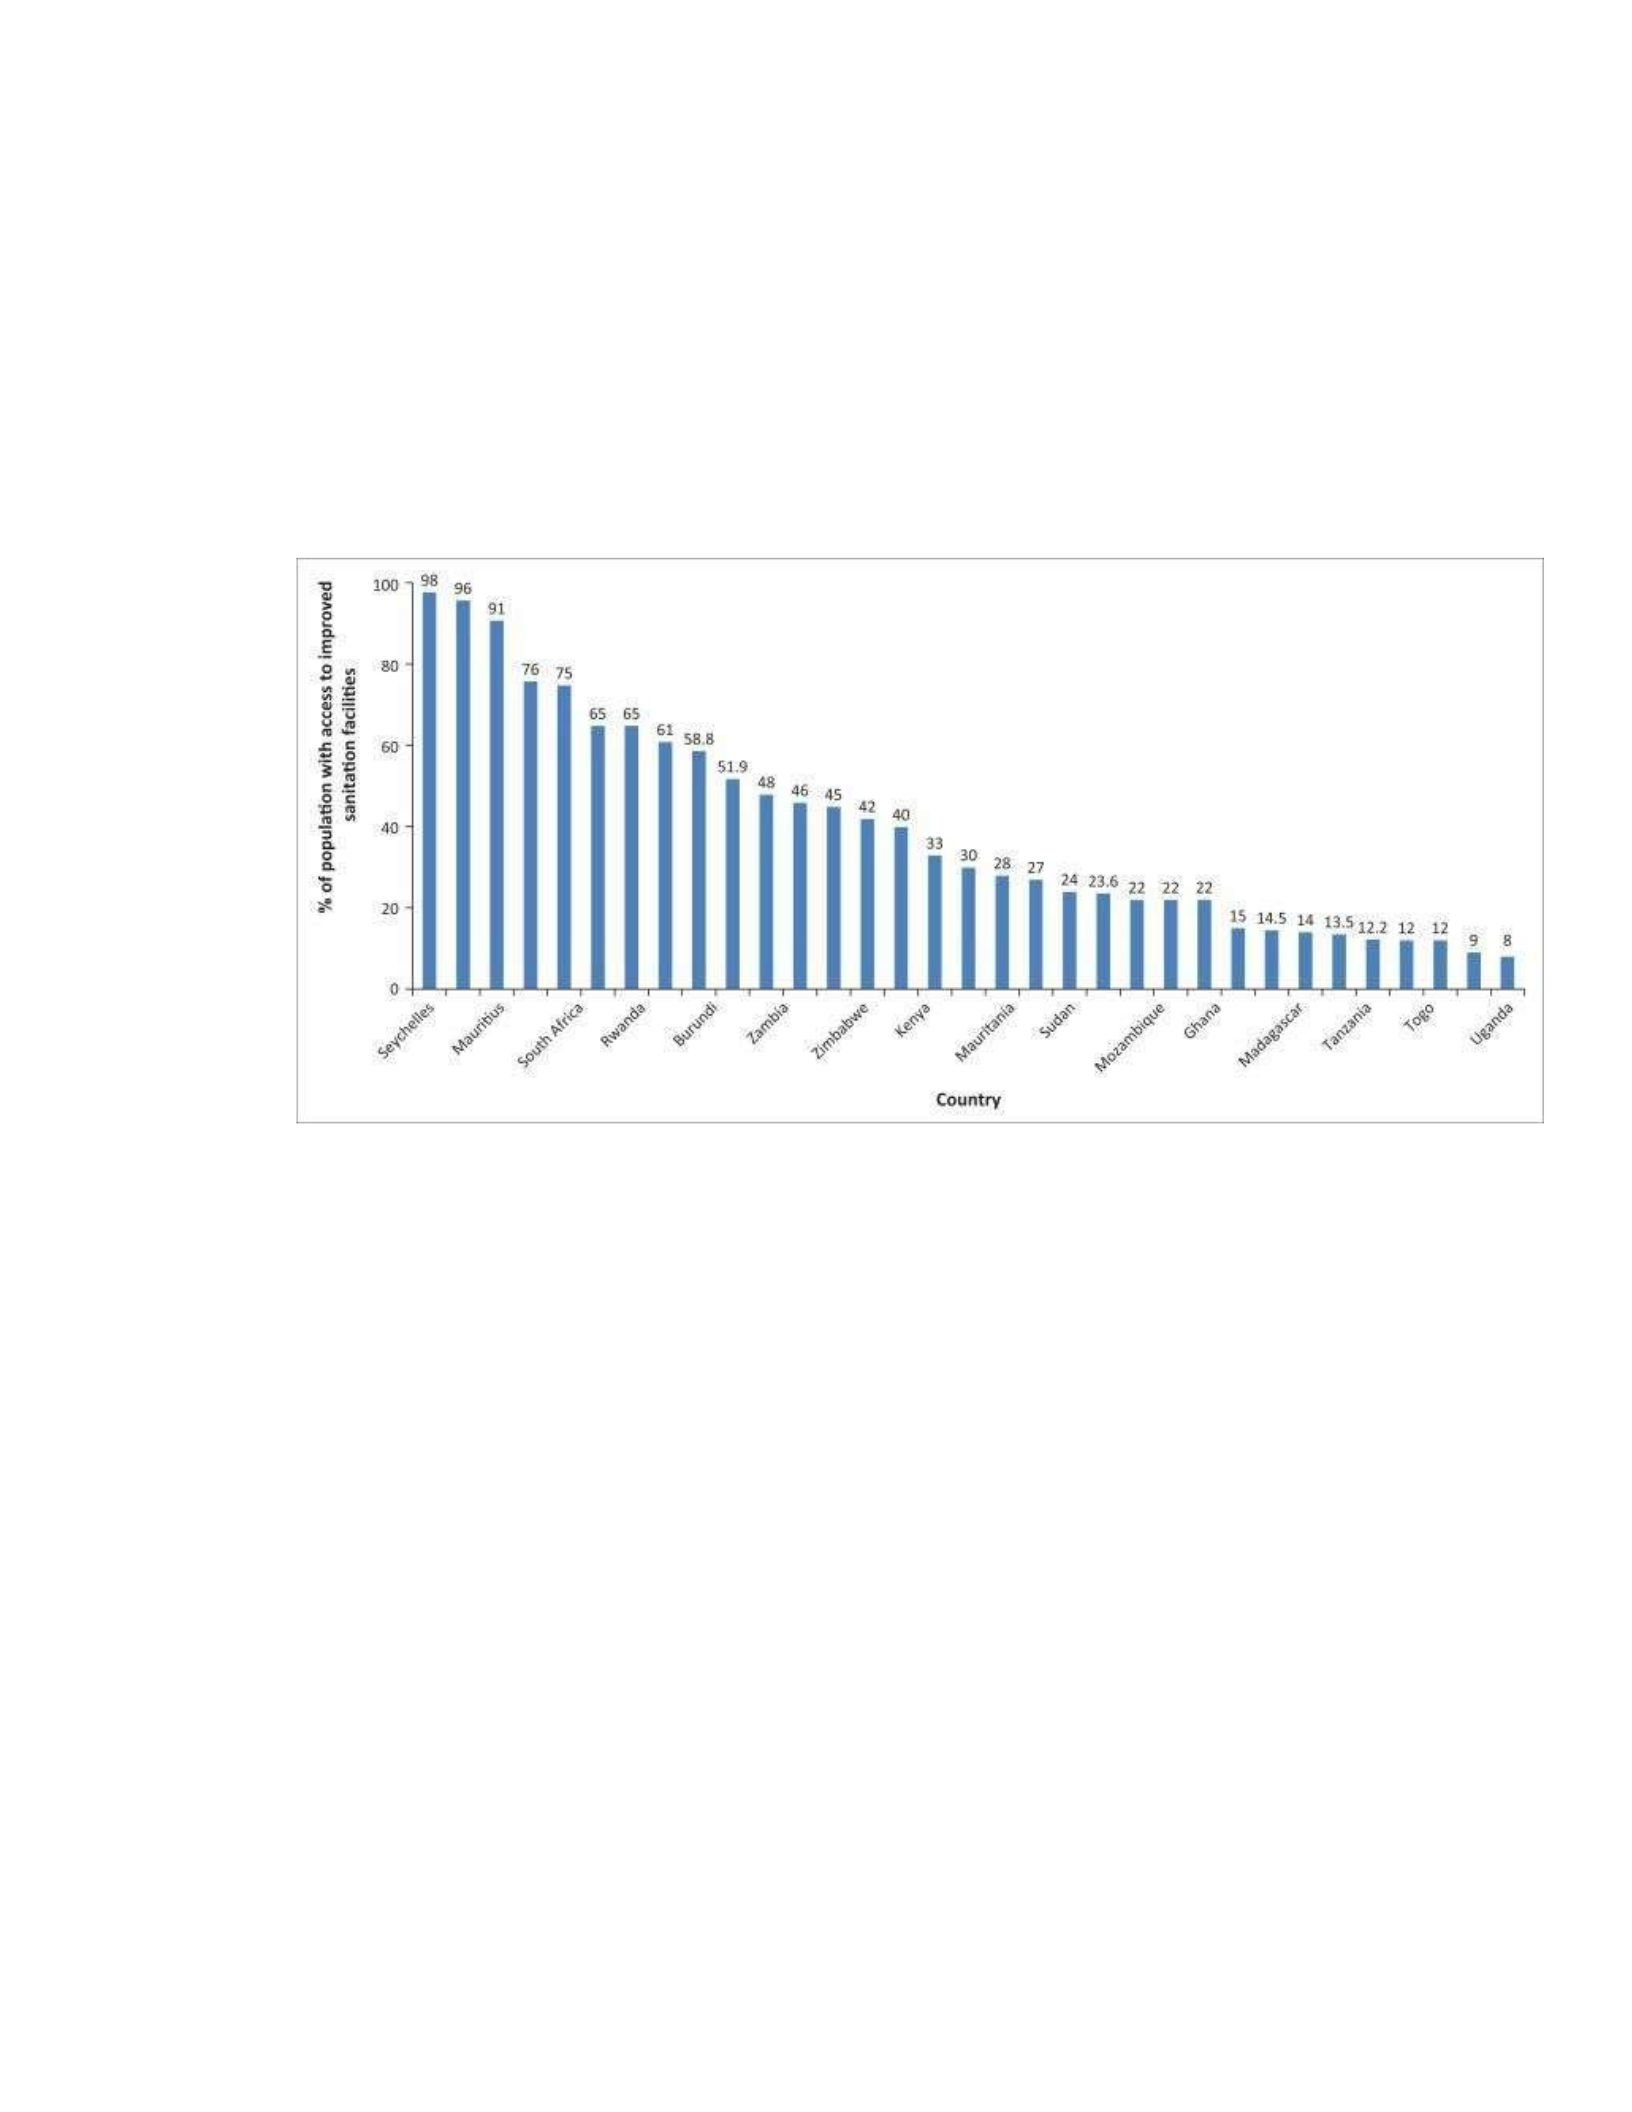
Similarly, Figure 3 showed the magnitude of improved sanitation in the most
successful African nations e.g., Morocco, Egypt, Botswana, Seychelles, Mauritius, and
South Africa that have had substantial progress. However, Chad, Uganda, Eritrea, Benin,
Togo, Niger, Tanzania, and Madagascar had the worst level of achievement for access to
sanitation (Alemu, 2017). In a similar perspective, Angoua et al. (2018) examined the
magnitude of access to proper WS facilities in Abidjan and assessed factors associated
42
with accessibility. According to the investigators, while 91.5 % of the urban population
can access improved drinking water, only 31.7% can access improved sanitation sources.
Figure 3
Improved Sanitation Facilities (percentage of population with access) in Africa in 2010
Source: Alemu, 2017.
In addition to the factors described above, socioeconomic conditions and the
socio-political crisis of the population influence WaSH and associated morbidity and
mortality (Angoua et al., 2018). For example, the increasing urbanization rate, the recent
civil war, and the rural exodus of the population in Abidjan have had a huge impact on
the population's well-being and overall health. Moreover, due to the extreme poverty of
rural inhabitants, they often move from rural areas into cities for a better livelihood.
According to WHO, UNICEF (2014), conditions of life, access to water, sanitation, and
infrastructures are bad in rural places compared to cities. Despite substantial progress,
both uneven and steady, about 96 % urban versus 84 % rural used improved water

43
sources; while 82 % of urban versus 51 % rural population used improved sanitation in
2015 (Darvesh et al., 2017).
For all these reasons described above, Angoua and associates suggested more
innovative planning approaches tailored to each population characteristics, needs, and
conditions context-based, for speed progress in accessing WS by 2030 as recommended
by the SDGs. Therefore, these strategies must implicate the following: local
administrative authorities, religious communities, and WaSH. While the dire studies
indicated meaningful information for child survival overall in Africa; yet the burden
caused by the huge rate of U5M in Cote D’Ivoire needs to be examined and understood
(Anguan et al., 2018).
Diarrhea is One Main Causes of Death Among Children Under 5
As mentioned repeatedly, diarrhea is one main cause of mortality and morbidity in
childhood (Darvesh et al., 2017; Pink, 2013). Diarrhea is in fact, classified as the second
predictive morbid risk factor among children below five (Baker et al., 2014). Poor WaSH
conditions are the primary exposure pathways for infection. Most particularly, in
disadvantaged regions, about 3/4 million children are killed by severe dehydration
associated with diarrhea occurrence. Often diarrhea can induce long-term damage to the
gut, growth stunting, and malnutrition (Baker et al, 2014). The enteric pathogens of
diarrhea (i.e., bacteria, viruses, and parasites) are transmitted through poor hygiene and/or
infected drinking water or food. As Baker and associates suggested, improving conditions
in WaSH may more likely minimize risks of exposure to infectious agents and reduce
incident diarrhea in childhood. For instance, about 36 % decline in diarrhea risk is

44
associated with improved sources of sanitation (Baker et al., 2014). The same view is also
supported by Darvest et al. (2017). Similarly, to the above view, Darvesh et al.(2017)
added that poor WaSH status and interventions can affect children development and
growth in many ways and is consensually acknowledged that without improving WaSH
conditions, improvement in undernutrition would not be feasible for the disadvantaged
children around the world. Below, I discuss several studies about diarrhearelated burdens
and other covariates of WaSH.
Studies About Diarrhea-Related Burden and Other Covariates of WaSH
In this quantitative study, Alemu (2017) conducted a study aimed to examine the
magnitude of the IMR under-five age empirically and systematically across African
nations in relation to improved sanitation accessibility .The investigator enrolled a total
of 33 nations between 1994 to 2013 in Africa. Using Durbin–Wu–Hausman specification
test, fixed-effect model, and Praison–Winsten regression with corrected
heteroscedasticity, the researcher verified results consistency (Alemu, 2017). The author
found out two IMR was averted when access to improved sanitation is increased to 1%
.Substantial decrease of IMR was highly associated with improvements in education,
health, and sustainable economic growth. While Alemu's study focused on the
accessibility of improved sanitation in Africa, the following research by Fink et al. (2011)
has examined access to WS and child health. Taking into consideration both independent
variables, more holistic results could be found pertaining to the determinants of child
mortality and WaSH related issues.

45
In their research, Fink, and associates merged DHS data with water and sanitation
information containing complete birth histories of children captured in these surveys.
Using logistic regression, the authors measured the impact of WS on both infant and
child death, stunting, and diarrhea. They found lower mortality with improved sanitation
(OR = 0.77), a lower risk of diarrhea (OR = 0.87) and a lower risk of mild or severe
stunting (OR = 0.73). In addition, a lower risk of diarrhea (OR = 0.91), a lower risk of
mild or severe stunting (OR = 0.92) were associated with access to improved water (Fink
et al., 2011). This study indicated slight protective effects (point estimates) than reported
estimates in the literature. Moreover, these results strongly underlined a significant health
impact of children in low-and middle-income nations without access to water and
sanitation (Fink et al.,2011). The results can be understood as infant children generally
get most of their nutrition from breastfeeding; hence, this may probably minimize their
direct exposure to the effect of sanitation and water. These two groups of the literature
showed convergent results in the sense that both indicated a direct association between
sanitation and child mortality (under 5), with a negative correlation between U5MR and
accessibility to improved sanitation.
Unlike the literature above, Darvesh and colleagues (2017) were interested in
intervention on WaSH and its impact on childhood morbidity. Using a systematic review
Darvesh and colleagues assessed the impact of WaSH programs and diarrhea in children
below five. They found in the pooled analyses, a decrease in incident diarrhea in point-
ofuse water filtration (RR: 0.47), point-of-use water disinfection (RR: 0.69), and hygiene
education (RR: 0.73). High heterogeneity levels were observed in pooled analyses. In

46
addition, improvements to water disinfection and the water supply at source have not
shown a significant risk of diarrhea, “nor did the one eligible study examining the effect
of latrine construction” (Darvesh et al., 2017, p.1). Various WaSH interventions have
indicated about 27% to 53% on diarrhea risk reduction in children less than five. The
authors suggested further research to examine the impact of these programs accurately
and context based (Darvesh et al., 2017). Hopefully, longitudinal studies may bring some
more light in these interventional outcomes.
Unlike the above, the following study related to diarrhea is more experimental (a
cluster-randomized trial: CRT) to explore the impact of school-based WaSH programs on
outcomes associated with diarrhea among children (younger siblings of school-going
children). Dreibelbis et al. (2013) conducted a CRT during 2007-2009, with the
enrollment of 185 schools in Kenya. The authors assigned to schools (based on the
availability of water) of two study groups. Using logistic regression estimated changes
between groups (Dreibelbis et al., 2013).The authors found out, among water stretched
schools, improvement in WaSH holistically were linked to a reduction of the odds of
diarrhea (odds ratio [OR] = 0.44; 95% confidence interval [CI] = 0.27, 0.73) and visiting a
clinic (OR = 0.36; 95% CI = 0.19, 0.68), relative to control schools (Dreibelbis et al.,
2013). There was no statistical difference in the groups with high access to water; water
treatment interventions; school sanitation improvements; and school hygiene promotion
was not linked with differences in prevalent diarrhea between control and intervention
schools (Dreibelbis et al., 2013). Finally, the investigators concluded that in

47
waterstretched places, intervention for WaSH in school with robust water facilities
improvements can minimize diarrhea illnesses in childhood (Dreibelbis et al., 2013).
Similarly, to the above, the Human security perspective suggested that water,
sanitation, and the health of children is correlated (Pink, 2013). Other literature supports
this worldview including Alemu (2017) who noted that access to improved WS are
necessities for all humans and this could have saved millions of infants from death before
reaching five years and beyond. Additionally, such improvement can reduce disparity
towards gender and vulnerable people. Yet, improper sanitation and open sewage systems
often severely contaminated sources of water leads to waterborne illnesses and death
(Pink, 2013). Given these pieces of evidence, many water- stretched countries have
incorporated water and sanitation programs to their health promotion effort in their
development goals and plans. For instance, The Millennium Development Goal 4
(MDG4) provides strategies to tackle the issue, reduce the morbidity, and mortality
among affected children ; by scaling up and promoting targeted programs. Providing and
making access to WaSH programs could promote health and the wellbeing of vulnerable
communities (United Nations, 2015). These programs should be considered as a control
measure: primary and primordial preventative strategies that may alleviate the onset of
waterborne and foodborne diseases, and related premature death of affected communities
(United Nations, 2015). However, to be effective, such programs need to identify and
target appropriate risk factors, risky behaviors, and vulnerable individuals (CDC, 2012)
and populations. Some examples of interventions about WS are presented in several
studies below.

48
The Relationship of WaSH and Child Morbidity and Mortality
The following research focused on the impact of WaSH and diarrheal diseases
among children. Using a cross-sectional survey, Diouf et al. (2014) examined prevalent
diarrhea and related exposure factors among children below 5 in rural Burundi. The
authors enrolled 903 children living in 551 households. Their results indicated that 33%
of children had diarrhea,46% used improved water facilities, and 3% had access to
improved sanitation. The authors found a lower prevalence of diarrhea among those
linked to caretakers with education in hygiene (18%), and boiled water (19%). In sum,
they concluded that the prevalence of diarrhea can drop through hygiene education and
household water treatment. Therefore, they suggested an ongoing hygiene education in
households and communities for a greater impact on children's health (Diouf et al., 2014).
Rather than a correlational design, a prospective design was used by Gorter et al.
(1998) to investigate the influence of hygiene practices on diarrheal diseases in children
less than two years old in rural Nicaragua. They selected 172 families (about 50 percent
had children experienced higher diarrhea rate and 50 percent with a lower rate) and
observed hygiene behavior over two mornings and recorded an episode of diarrhea
weekly for five months. The investigators found that diaper/underclothes, domestic
cleanliness, and hands washing had the highest protective effect. Better economic
position (i.e., possession of radio) and schooling (>3 years of primary school) had a
positive impact on general hygiene behavior. The presence of radio leads to a slightly
stronger effect. Finally, the researchers consistently found a linkage between almost all
hygiene practices and diarrhea, more years of education were associated with better

49
hygiene behavior (Gorter et al., 1998).This study resonates with previous literature with
regards to morbidity such as diarrhea incidence and its association with hygiene
behaviors, based on SES and education.
The following study by Messou, Sangaré, Josseran, Le Corre, and Guélain (1997)
took place in Cote d’Ivoire. The researchers compared two groups of villages to explore
compliance influence and hygiene, water facilities: and oral rehydration for diarrheal
diseases among children less than 5 in four villages. The researchers compared children's
diseases and death rates in two groups of villages (with and without intervention) before
and after the intervention. Baseline survey provided data on diarrhea incidence and
mortality rates. The authors found a 50 % reduction of diarrhea incidence rate and 85 %
reduction of death associated with diarrhea in the intervention villages. Hence, they
concluded that access to improved water and hygiene played a critical role in preventing
diarrhea among children (Messou et al.,1997).
A similar study was conducted by Rasella (2013) in Brazil to examine the Water
for All Program (PAT) program impact in 224 counties. The aim of PAT is to expand
WS sources coverage in areas with high exposure vulnerability to waterborne illnesses.
The author compared data collected before-and-after interventions from 2005 to 2008 and
found out that coverage of PAT was inversely linked (p < 0.01) to the U5MR. Countries
with a PAT coverage over 10 percent had a reduction of 39 percent (p < 0.05) in
mortality from diarrhea, U5MR of 14 % (p < 0.01), and hospitalizations induced by
diarrhea of 6 percent (p < 0.05) when compared to counties without PAT or with lower
coverage. Therefore, the investigators concluded that in highly vulnerable settings

50
programs for water and sanitation could have a significant influence in reducing health
inequalities. This resonates well with previous literature as Angoua et al. (2018)
emphasized earlier. In a conclusive tone, Angoua et al. noted that despite all the progress
done to achieve access to safe WS sources; still these elements are still challenging for
SSA nations.
In an attempt to explain what triggers access to WS in these regions, Angoua et
colleagues through a correlational study examined the ability to access improved
sanitation and water in urban settlements habitants to identify factors that predict access
to guide to address environmental risks and associated health issues (Angoua et al.,
2018). The authors undertook a cross-sectional study design in six poor settlements of
Yopougon. They randomly selected 556 households through logistic regression modeling
to explore potential links between access to improved water /sanitation. They found out
that about 25 % of all households did not have access to clean water and 57 % without
improved sanitation. In peri-urban areas, characteristics of these settlements and
socioeconomic status were the main predictors for poor access to reliable sanitation and
water services. In addition, having a household head’s spouse was 3.57 more likely to get
access to clean water than the absence of a household head wife; hence, emphasizing the
importance of women in sustaining clean water at home in these particular areas. In sum,
the authors suggested that women should be engaged at all levels of programming for
promoting water in these places to enhance the population’s well-being. While religion
does not appear to play an important role in access to sanitation and water; successful

51
“interventions should involve religious communities because of their large
representation” (Angoua et al., 2018, p.1).
Similar research took place in Kenya, by Bocquier, Beguy, Zulu, Muindi, and
Konseiga (2011). In this research, the investigators examined the impact of child
migration and mother on children's survival (more than 10,000) residing in informal
congested settlements (slums) in Kenya, without inadequate access to health care, safe
water, sanitation, and other social services. Their results showed slum -born children have
a higher mortality rate compared to non-slum-born counterparts. Furthermore, slumborn
children at migration time, have the highest mortality risk. Despite the similarity in the
SES of the study population in different geographic settings; however, while the previous
study focused on poor peri-urban settlements in West Africa City (Abidjan,
Côte D’Ivoire); the study of Bocquier et al. (2011) has explored survival (through child
mortality rates) among slum-born children compared to non-slum-born in Kenya.
Angoua et al. (2018) have examined accessibility to WS in Cote D’Ivoire,
however, they restricted their study on water and sanitation alone. Expectably, by
exploring morbidity and or mortality, a subsequent endpoint could have been very
insightful for my study.
Other studies assessed the contribution of the effects of political, economic,
social, economic, health programs, policy, and health systems in reducing U5MR (Feng
et al., 2012). This study examined secondary data on China Health Statistics Yearbook
data (from 1990-2006) in 30 Chinese provinces. They conducted regression models to
assess the effect of thirty-five factors and five constructs defined by factor analysis. The

52
result indicated that China U5MR has declined from 65 to 21 per 1000 live births and
achieved the MDG4 nine years earlier. The five constructs examined, predict about 80 %
of the variability in mortality rates among children less than five across provinces over
the seventeen years period (Feng et al., 2012).
Finally, the authors concluded that health systems strengthening, and vertical
interventions or growth are insufficient to reach expectations in reducing child death
while improving key social determinants of health still lagging. Therefore, to improve
progress toward MDG 4, a cross-sectoral approach (e.g., improving access to safe
sanitation, clean water, and promoting maternal education) may more likely lead to the
greatest impact on U5MR in low- and middle-income countries (Feng et al., 2012).
In Kenya, similar research was undertaken by Garrett et al. in 2008. The
researchers compared the rates of diarrhea in 960 under-five children in 18 randomly
selected villages (six comparisons versus 12 intervention) and 556 households. Over an
8-week period, the authors conducted home visits every week to evaluate the effect of the
household latrine, water treatment, shallow wells, and rainwater harvesting on incident
diarrhea among children less than five. Multivariate analysis indicated that living in an
intervention village, using rainwater, and the presence of latrine, were independently
linked to minimal risk for diarrhea. Diarrhea risk was higher among shallow wells users.
In sum, the researchers concluded that using latrines, rainwater, and chlorinating stored
water minimized the risk of diarrhea and that combining interventions may improve
health outcomes.

53
Rather than a simple observational design, Cha et al. (2015) work was
experimental; most specifically, a cluster-randomized study design undertaken in Ghana.
Such designs could have a lesser threat to validity when careful and rigorous protocols
are followed. In fact, the authors conducted this research to explore the impact of
improved water services on prevalent diarrhea in children below five years in Ghana.
Studies exploring the influence of improved water sources; mostly inadequately used
randomized trials or observational designs. As described in the early section, Cha et al.
(2015) used a modified Poisson regression to measure the prevalence ratio, coupled with
an intention-to-treat analysis. Overall, the results showed that improved water sources are
more likely to decrease diarrhea risk by 11% in children less than five (Cha et al., 2015).
Their study has been instrumental in shedding some light regarding the matched cluster
randomized control trial, with a careful methodological approach to convey the evidence
to support their findings. However, it only focused on incident diarrhea as the outcome;
while hopefully, I would have expected to go further by assessing some final endpoints
e.g., mortality. Hence, not to be restricted to water sources only, but sanitation, hygiene,
and all potential exposure factors captured in the DHS data for instance.
Summary and Conclusions
The review of the literature about WaSH and associated risk factors on U5MR
revealed the public health significance of the problem, its magnitude, its economic , and
social burden associated with high disparities based on geographic setting and
socioeconomic conditions of the affected population. Thereby, the reasons why WaSH
needs must be addressed through access and provision to adequate sanitation, clean water,

54
and hygiene. In fact, the literature showed that lack and limitation of water and proper
sanitation; as well as subsequent contributing factors e.g., lack of proper hygiene was
among exposure factors repeatedly associated with the high U5MR and morbidity in
children below 5 mainly in disadvantaged places located in Asia, Latin America, and
Africa .As mentioned in the early section, globally, lack and limitation of water affects
more than 40 % of the population, an alarming figure that is expected to increase with the
effect of global warming .This alarming public health problem poses a serious threat to
the life of the local population; most particularly, children.
In sum, these studies have relevant insightful evidence derived from meticulous
designs (i.e., cross-sectional descriptive and analytic; experimental, RCTs; systematic
review; and meta-analysis). Yet the current review will not only inform the choice of my
research methodology, design, methodology, and analysis, but also, will examine other
risk factors besides WaSH e.g., diarrhea, the geographic settings, SES, geographic
settings, and sociodemographic characteristics that may influence U5MR. Not only the
literature above focuses on young children (under 5), their burdens such as morbidity
related to access to poor WaSH , but also, most of them use a quantitative paradigm with
programs/interventions provided to the disadvantaged communities of Asia, Latin
America, and Africa. Although, the majority of these findings are not directly from Cote
D’Ivoire (the setting of the current study); yet, they provided insightful information about the
magnitude, the public health significance, the risk, and contributing factors associated with U5MR; and
the impact of involved interventions/programs on the health and wellbeing of the target population. The

55
review above showed the discrepancies related to the high death rates in children under 5, WaSH, and
other risk factors in Cote D’Ivoire.
However, it is still unclear how to link the high mortality rates in Cote D’Ivoire despite
all the efforts done to minimize this issue of public health importance.
Chapter 3 discussed the study method, design, and rational; sampling and
sampling procedure; the target population; and data collection procedures e.g., ethical
procedure, data gathering or access to the secondary data; and threats to study validity.

56
Chapter 3: Research Method
Chapter 3 describes the study design and rationale; the research methodology; the
study population; the setting; the recruitment strategy; the sample size estimation through
power analysis; the inclusion and exclusion criteria; the research questions and
hypotheses; the sampling method; the instrumentation and materials; the study variables;
access to DHS data; and statistical analysis plan. The section also introduces and
addresses potential threats to the study validity and provides a thorough explanation of
related ethical procedures and introduces Chapter 4.
Research Design and Rationale
Research methods and designs are critical elements to consider during the
planning, design, and implementation of the research study. The current study was a
secondary analysis using pooled Cote D’Ivoire DHS data by merging all available data
sets from 2005-2020 at the time of the analysis. The goal of this quantitative study was to
examine the magnitude of the association between the dependent variable (the mortality
of children under 5 years old) and the independent variables (access to improved water
sources, access to improved sanitation sources, and hygiene).
In this study, DHS surveys data and questionnaires, including the standard
household questionnaires through individual interviews with mothers about their
sociodemographics, socio-economic characteristics, their health behaviors, and health
outcomes; particularly related to their children under 5 years was used. Quantitative
inquiry is pertinent, as this approach can include measures (questionnaires) that these
mothers can answer for instance, the full birth histories of their children, information

57
about access to water, sanitation, and hygiene, and several covariates captured in the
pooled DHS data.
Additionally, in cross-sectional designs, all variables are captured at once
(Creswell, 2014). Often the design of a study drives data collection methodology and data
analysis; hence, users of such data are driven by the preexisting design set by the primary
data collectors/researchers and in fact, DHS captures data using a cross sectional design.
For instance, the proportion of those exposed and those not exposed to quality WaSH
variables and all other exposure factors captured in the DHS data will be measured to
describe the study population by the magnitude of death among children under 5
associated with the above risks, by time and geographic setting.
Moreover, this quantitative analytic cross-sectional approach can make inferences
to the population based on the estimates found from this quantitative inquiry. Unlike
traditional (gold standard) experimental designs, in cross-sectional designs, there is no
need to perform manipulation on the independent variables. In addition, there is no need
to assign to the study participants the measured conditions presumably seen as the effect
of the predictors on the dependent variable inferentially. One benefit of employing a
quantitative cross-sectional is that such designs can rely on existing differences rather
than fluctuation due to interventional effect, in addition to the fact that the selection of
groups will depend on existing differences rather than random allocation, and no time
dimension is a concern (USC, 2013). Quantitative methods can also provide numerical
analysis for a deductive system worldview. Furthermore, with quantitative methods,
biases, systematic errors, confounding, and interaction factors could be minimized or

58
controlled in many ways, whether at the design stage and or at the analysis stage through
weighing adjustment, stratification, and use of multivariate analysis (Pike, 2008). As Pike
(2008) suggested, through weighting adjustments, researchers can compensate for biased
estimators led by survey nonresponse. Following this perspective, using this design
(cross-sectional), I can still make an adjustment through weighting to compensate for
nonresponse rates and missing data in this data set (the DHS). In an analytical
crosssectional approach, I conducted a survival analysis such as cox proportional hazard
method to minimize biased estimators while adjusting for any spurious variables (i.e.,
confounders and effect modifiers) so that more accurate estimates could be achieved with
more valid and reliable results associated with high replicability and generalizability
(Health Knowledge.org, n.d.). Furthermore, cross-sectional designs are relatively less
expensive, easy to implement, and a time-saving approach as compared to sophisticated
experimental designs, e.g., RCTs.
I looked at the level of access to WaSH and all confounders and or interaction
variables simultaneously in the study population, women, and their children under 5
exposed to such environmental risk factors. Therefore, as mentioned earlier, the
crosssectional designs are relevant for such an objective to measure trends and strength of
the association between the independent and the outcome variables involved in this
research study both descriptive and inferential. In fact, this design helps for the
advancement of knowledge in the realms of the social sciences by providing a basis to
describe patterns of association or correlation between variables (Frankfort-Nachmias &
Nachmias, 2008).

59
Moreover, the quantitative cross-sectional design helped to enroll a large sample size in
this study which may increase the research external validity and power (Burkholder, n. d.;
Crosby et al., 2006; Ellis, 20110; Forthofer et al., 2007; Frankfort-Nachmias et al., 2008).
Using a cross-sectional design, I examined the strengths of the relationship between the
study variables and examined the determinants of U5MR in order to further contribute to
the knowledge about WaSH and other contributing risk factors that led to the huge
U5MR. Despite all the advantages of this design, as a correlational design, cross-
sectional studies present some weaknesses in the sense that they cannot ascertain a
temporal linkage between outcome and predictors variables, so causation cannot be
assessed effectively in such designs (Frankfort-Nachmias et al., 2008; Sullivan, 2012;
Szklo & Nieto, 2014).
The goal of this correlational study is to uncover how and to what extent the
under 5 mortality is affected by WaSH. The rationale behind this research study is
distinctive as it aims to tackle an under-researched subject in public health realms
focusing on the experiences of affected mothers pertaining to the loss of their children
before reaching 5 years old —more particularly, among the female strata of the
population at reproductive age, ranging from 15-49, who have been underrepresented in
the literature, and those disadvantaged populations who may be disproportionately
affected in various instances e.g., gender, health, and SES. The main purpose of this
quantitative cross-sectional study is to address the research questions below: RQ1: To
what extent does access to improved sanitation facilities affect the under-5 mortality
among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables?

60
H01: There is no statistically significant difference in the under-5 mortality while
controlling for demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved sanitation facilities and
those without.
HA1: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved sanitation facilities and
those without.
RQ2: To what extent does access to improved water sources affect the under-5 mortality
among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables?
H02: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources and those
without.
HA2: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources and those
without.
RQ3: To what extent does adequate hygiene affect the under-5 mortality among women
15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and maternal
variables?

61
H03: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among women
15-49 in Cote D’Ivoire with adequate hygiene and those without. HA3: There is a
statistically significant difference in the under-5 mortality while controlling for the
demographic, socioeconomic, and maternal variables among women 15-49 in Cote
D’Ivoire with adequate hygiene and those without. RQ4: To what extent does access to
improved water sources, improved sanitation facilities, and adequate hygiene affect the
under-5 mortality among women 15-49 in Cote
D’Ivoire while controlling for demographic, socioeconomic, and maternal variables?
H04: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources, improved
sanitation facilities, and adequate hygiene and those without.
HA4: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources, improved
sanitation facilities, and adequate hygiene and those without.
Methodology
This study used a quantitative correlational method, specifically a cross- sectional
design, using pooled data from several DHS survey years between 2005 and 2020 by
merging all available data sets at the time of the analysis.

62
Population
Cote D’Ivoire is in Western Africa, bordering the North Atlantic Ocean, between
Liberia and Ghana. Its current population is 27,481,086 people with a population growth
rate of 2.26%. In 2018, this country had about 25,009,229 (Central Intelligence Agency,
n.d.). The population of Cote D’Ivoire was about 18,354,514 in 2005 and 22,6 million
people in 2011 with a growth of 2.6% and more than 60 ethnicity categorized in five big
groups (National Institute of Statistics, & ICF International, 2012). Life expectancy is
about 61.3 years for the total population with a death rate of 7.9 deaths/1,000 population
and ranked 93rd in the worldwide comparison (Central Intelligence Agency, n. d.).
Sampling and Sampling Procedures
The present study enrolled all women between 15 and 49 years who were living in
Cote D’Ivoire at the time of the surveys; hence, all the remaining people e.g., age ranging
under 15 and those more than 49 years old were automatically excluded from this
research. The selected participants were interviewed in their house regarding their
childbirth story, number of children under 5, child’s birth date, child’s survival status,
reason for child’s death, and child’s age at death.
The Sampling Strategy and Design
Scientific sample surveys are a reliable and cost-efficient approach to gather
population-level data e.g., demographic, health, and social data. The MEASURE DHS
project is a worldwide project implemented by many various countries and at various
points in time within a country. To reach best quality, consistency, and comparability in

63
survey results, sampling activities in the DHS are being guided by several general
principles. The key principles of DHS sampling include:
● Use of an existing sampling frame
● Full coverage of the target population
● Use probability sampling
● Use an adequate sample size
● Use the simplest design possible
● Conduct a household listing and preselection of households
● Provide good sample documentation
● Maintain confidentiality of individual’s information
● Implement the sample strictly as designed (ICF International, 2012a).
This study used quantitative sampling such as a cluster sampling design in which
the unit of sampling is a group of population elements (not a single element of the
population). The unit of the sample encompasses all those align with the inclusion criteria
of the study (Frankfort-Nachmias et al., 2008), and this is expected to be households with
at least one woman (a mother, a caregiver, or child-bearer) ranging from 15-49 years old
living there in Cote D’Ivoire. To better assess the magnitude of the relationship between
WaSH on children under 5 years’ mortality, the most reliable source of information is the
caregivers (often mothers) and or any childbearing women between 15 and 49 years old,
living in randomly selected households at the time of the surveys.
Frankfort-Nachmias et al. (2008) suggested that the sampling design affects data
gathering and quality. Quantitative sampling such as a multistage cluster sampling design

64
was the most relevant method for this research to examine a representative mortality rate
for the country. According to Johns Hopkins Bloomberg School of Public Health (2009),
cluster sampling is also relevant for huge-scale studies. The cluster sampling is
appropriate and cost-efficient with a sampling frame readily available at the level of the
cluster. This design is less time consuming and suitable for institutional surveys, as well
as for listing and implementing. A stratified two-stage cluster design was the sampling
design employed for DHS. A two-stage cluster sampling procedure in which the cluster
represents a group of adjacent households which serves as the PSU for field work
efficiency. Often a cluster is an enumeration area (EA) with a measure of size equal to the
number of households or the population in the EA, drawn from the population census
(ICF International, 2012a).
The first stage (at the EAs) is often derived from Census files, the second stage in
each EA selected, and a household’s samples drawn from households list (Demographic
and Health Surveys, 2018). Moreover, the sample is generally representative of both the
national, residential (rural and urban), and regional (states and departments) levels
(Demographic and Health Surveys, 2018).
Steps for Sampling and Sample Size
● A random selection of a representative group of districts (from the most
recent list) of the Cote D’Ivoire ministry of interior was done first,
● Then, a random selection of representative villages/blocks from every
selected district was done,

65
● Then, a random selection of a representative number of households in
selected blocks/and villages,
● Finally, an interview of all women from 15 – 49 years in their home.
● A power analysis will help to compute the minimum sample size to expect a
statistically significant result (Ellis, 2010; Lakens, 2013). Because the DHS
surveys have huge sample sizes (between 5,000 and 30,000 households) (ICF
International, 2012b), I used the complete data set for the secondary analysis.
The DHS sampling is already done before data has been collected for
interested users like me. So, there is no real need to do an analysis; however, a
posteriori power analysis can be done just to align the existing sample size
and the minimum expected requirement. In fact, four key parameters are
included in the computation of the sample size e.g., the effect size, the alpha
level, the study design/type, and the statistical power. The alpha (α) is set by
the researcher. While statistical power is the probability that a given statistical
test will detect a real relationship or treatment effect between variables .The
effect size represents the magnitude or strength of the relationship between
two variables, it can be measured by the ration or difference. For instance,
odds ratios (OR) comparing the likelihood of the same occurring event within
two separate groups, or Relative risk (RR) also known as risk difference
(Sullivan, 2012).
● For the purpose of this study, all women from15 to 49 years old living in a
household located in Cote D’Ivoire are considered as potential participants.
The following are the assumptions I made:

66
● Alpha is 0.05
● Confidence level of 95%
● Power level 80%
● The confidence interval of 2.5% (to detect a difference of 25 per 1000
mortality rate 123 per 1000). After entering the parameters listed above, I
selected a sample size to estimate the minimum sample size based on the
criteria and assumptions made earlier. Both the plot and its numerical display
associated with G Power sample size calculation are shown. As seen in Table
3, at 95% confidence level and a CI of 2.5%, I am expected to draw a
representative and unbiased estimate with regards to the study effect or
outcome (U5M) under investigation by reaching and interviewing a total of
2,184 women (15-49 years) living in randomly selected households in Cote
D’Ivoire.
Table 3.
Sample Analysis
Input:
Tail(s) Effect
size d α err
prob
=
=
=
Two
0.12
0.05
Power (1-β err prob)
=
0.8
Allocation ratio N2/N1
=
1
Output: No centrality
parameter
=
Critical t
Df
Sample size group 1
Sample size group 2
2.8039971
=
=
=
1.9610518
2182
1092
1092
67
Total sample size
=
2184
Actual power
=
0.8003305
t tests – Means: Difference between two independent means (two groups)
Figure 4
Plot for Sample Analysis through G-power
As shown in Table 3, power (1-β err prob) =0.80, this implies that I decided to get
80 % power to make an inference from these parameters to the population statistics. And
power equals one minus beta (type 2 error), this shows the correlation between them and
as both beta and power are inversely corrected (Ellis, 2010; Lakens, 2013).
Yet, empirically, the sample size for this study was based on all the
available data from 2005 to 2020 merged for a newly pooled database ; however,
each survey has been conducted individually; so, there was a sampling for each
of these surveys accordingly. All the surveys from 2005-2020 used a stratified
two stage cluster design for sampling. All the Cote D’Ivoire DHS surveys were
representative at the national level. With regards to the sampling ,for instance, the
2005 surveys used 10 old administrative regions and represent the 19 actual

68
regions constitute with the city of Abidjan .The 11 geographic strata were
retained, then these were stratified in urban and rural zones for the sample strata
.There was a total of 21 strata in the sampling (National Institute of Statistics, &
ICF International, 2005). In the first stage, a sampling random selection was done
independently of each stratum. In the second stage, an independent selection was
done in each primary unit from the first selection (first stage). Census districts
have been systematically and randomly selected from each stratum with
proportional probability at the level of census districts as the number of
households. In the second stage, a fixed number of households were selected
from the regional district (DR) randomly and systematically with equal
probability of selection. So, in total, 20 households in each DR have been
retained. All members of these households were identified with the household
questionnaire for the survey. All women and men aged 15-49 were surveyed via
the individual questionnaire (National Institute of Statistics, & ICF International,
2005).
The 2005 Cote D’Ivoire DHS survey was undertaken between August to October
2005, 4 573 households ,5 183 women and 4 503 men aged 15-49 were successfully
interviewed .In detail, a national sample of 4 980 households were selected ,with 20
households for each DR , 249 East/DR were selected at the first stage at the national
level. With 109 in urban versus rural 140.The repartition of clusters and households
surveyed successfully has been calculated per region and residence. In total the DHS-CI
for the 2005 survey had enrolled 247 clusters out of 249 planned for a total of 4 998

69
households. Among the 4 998 selected households, 4 573 have been identified and 4 368
were effectively and successfully surveyed with 95,5 % response rate (National Institute
of Statistics, & ICF International, 2005). Overall, the household survey in DHS 2005, has
determined 5 772 eligible women aged 15-49 for the individual survey and 5 183 among
them have been successfully surveyed with 90 % response rate (National Institute of
Statistics, & ICF International, 2005). In sum, 5183 was the sample size for women 15-49
for the 2005 survey.
With regards to the 2011-2012 survey, a total of 352 clusters were selected for the
Cote D’Ivoire DHS 2011-2012 , from this ,about 351 have been surveyed and only one
was inaccessible. From these selected clusters, 10,413 households have been selected
from this, about 9 873 occupied households were identified during the 2011/12 survey
(National Institute of Statistics, & ICF International, 2012). Among the 9873 households,
9 686 have been successfully surveyed (98 % response rate) with a slightly higher rate in
rural areas (99 %) versus (97 %) in urbans areas. Among the 9686 surveyed households,
10 848 women aged 15-49 years have been identified and eligible for individual survey
and 10 060 had a successful survey with a 93 % response rate (National Institute of
Statistics, & ICF International, 2012). Due to missing variables (hygiene) in the 2005
data, and the fact that expected 2019 data has not been completed, new data is expected
soon. Finally this study used merging data for 2011 and 2012.
Fortunately, these numbers, as displayed above, are a relatively huge sample size
aligned with the size of the general population and all the protocols used to derive such a
large number of participants in the surveys. Using a rigorous sampling strategy is key, yet

70
many types of threats to the study validity (external and internal) may trigger the study
accuracy, quality, and generalization. External validity is linked to the sampling size and
sample design; hence, to reach a large power level, using a relevant sampling design is
essential. This would increase the likelihood to reach a representative sample size which
may lead to an accurate inference or estimation of the population parameters (Lakens,
2013). In general, larger sample sizes are best to increase the ability to detect an effect;
however, while larger samples are better, sample sizes must be reasonable in size and cost
effective (Burkholder, n. d.). The next section discusses the recruitment approach and
data collection instrumentation.
Procedures for Recruitment, Participation, and Data Collection
As secondary data analysis, this study used pre existing data: The DHS data to
evaluate the strength of the relationship between U5MR and WaSH variables captured in
the merged DHS database. I followed the DHS protocol for data granting and retrieval.
More details were provided in sections below about the characteristics of DHS data,
ownership, and procedure to retrieve DHS data. I have not done a primary data
collection, but if this were the case I would have customized an existing questionnaire
from DHS (i.e., DHS household survey questionnaire) including open and closed-ended
questionnaires sent by postal mails, oral administration, and /or self-administrated..
Closed-end questionnaires are not only easy to analyze; however, open questions allow
more freedom to respondents to express their attitudes, thoughts, and emotions.
Administration of the questionnaire via mail could enroll a larger number of the women

71
aged 15- 49 in their home and it is low- price, less time consuming, convenient, with less
observation bias (McKenzie et al., 2013). However, this won’t be suitable for the target
population as many are not literate and do not have a mailing address (Pink, 2013).
Although online surveys have frequently been used in research because I opted
for existing data, there is no need for an additional online survey for a primary data
collection. Some advantages of online surveys include its low cost and higher speed than
most traditional methods of data collection (Ahern, 2005). In addition, online surveys are
convenient, easy, and inexpensive, etc. It also encompasses potential multimedia
elements such as videos and audio clips (Pew Research Center, 2016). Moreover, the
absence of interviewers in online surveys can relatively minimize biases (i.e., interviewer
bias and social desirability bias) than the traditional surveys approach (Pew Research
Center, 2016). Traditional surveys are more relevant in this case. The reality as related to
the socio-demographic characteristics of the priority population is the fact that they live
in rural and are underserved communities mostly, lacking basic natural resources. The
majority of them do not have access to the internet (Pink, 2013). Thereby, it will be
unsuitable to conduct an online survey for the target community. DHS program used
listing of the survey’s clusters and individuals through segmentation and stratification
approach (ICF International, 2012a; 2012b). This could also minimize certain biases (i.e.,
observation bias) as well as reach the selected study participants directly in their
household (McKenzie et al, 2013). Using a culturally relevant audience-centered survey
media to convey the survey questionnaire will more likely optimize the survey and reach
the selected population (Schiavo, 2007; Resnick, & Siegel, 2013). DHS program used

72
trained enumerators to administer interviews using standardized questionnaire
instruments to eligible individuals previously “selected in a scientifically designed
sample” (Measure Evaluation. Org. n.d., p. 59).
Prior to conducting the survey, the measurement tools have been examined and
pretested through a pilot study (ICF International, 2012a; 2012b). In fact, a pretest of
the questionnaire was also conducted in a few clusters not previously selected for the
main survey to assess the instruments (questionnaires) quality and ensure the
understanding of the translations by both the respondents and interviewers (ICF
International, 2012a). In addition, an Institutional Review Board (IRBs) were
submitted, granted after review in addition to ensuring all potential legal issues
associated with the research (waiver of liability or informed consent). These
documents were given to the study participants, were agreed upon, and signed (ICF
International, 2012a). The following section provides ample details about the
measurement tool.
Instrumentation and Operationalization of Constructs
It is important to develop or borrow the most relevant measurement instrument
with high reliability and validity to assess the variables under investigation to make
unbiased inferences evidenced by the research. To examine the relationship between
access to WaSH variables and their influence on U5MR; I used the Cote D’Ivoire DHS
data containing the full birth histories of the exposed children, WaSH information, and
several potential exposure factors expected to be examined. The main advantage of DHS
data is the fact that it enables to look at child mortality and many other factors associated

73
with child death e.g., socioeconomic, demographic variables, and other comorbidities
(Fink et al., 2011).The DHS is a nationally representative household survey mainly
funded by the United States Agency for International Development and implemented by
Macro International in collaboration with national statistical agencies (Fink et al., 2011;
ICF International , 2012 b). The standard DHS surveys have large sample sizes (between
5,000 and 30,000 households) and are routinely undertaken every five years to enable
comparisons over time.
For this study, the household questionnaire was used and information about WaSH
variables and other confounding variables were measured .The birth history contains
information on child death, date of birth, gender, child survival status (alive or died), and
child age at death. The DHS is an ongoing surveillance and monitoring system to collect
information in the household every five years across countries worldwide
(Demographic and Health Survey, 2018). “The data collection methodology consists of
trained enumerators administering interviews using standardized questionnaire
instruments to eligible individuals selected in a scientifically designed sample” (Measure
Evaluation. Org. n.d., p. 59). In the section below, I discussed the reliability and validity
of the measurement instrument.
Validity and Reliability of the Measurement Tool
Data quality of a survey directly influences the reliability of the estimates
produced. Investigators should ensure that the instrument truly measures what it intended
to measure. Using a valid instrument increases the likelihood that assessors would

74
accurately assess what is supposed to be measured. McKenzie et al. (2013) suggested the
following approach to ensure the measurement instrument validity e.g.,” face validity (in
observation), content validity, criterion-related validity, sensitivity and specificity, and
construct validity among others” (p.119). The authors emphasized that the instrument
validity can be affected by differences across individuals, therefore using an inter-rater
agreement (or observer agreement) must be considered and it is critical to reach a high
level of agreement). Moreover, validity can be more informally established in the form of
face validity consisting of asking a panel of experts whether the questions really measure
the intended concept. The agreement of those experts would determine face validity
establishment (Issel, 2009).The DHS program has taken precautionary approach prior to
data collection ; particularly, during pilot and pretesting stage to assess the quality of the
questionnaires (measurement instruments) (ICF International, 2012a; 2012b).
With regards to the instrument reliability it represents to the consistency of the
measurement process .Windsor et al (2004) defined reliability as an” empirical estimate
of the extent to which an instrument produces the same result (measure or score), applied
once or two or more times “(Overstated by McKenzie et al., 2013, p.118).Viewed as an
internal consistency, reliability would represent the inter-correlations among the
individual items on the instrument, e.g., are the instrument items are measuring the same
research domain? This is possible by examining the instrument to ensure that the items
reflect what it assumes to be, with the appropriate consistency with regards to the item's
level of difficulty (McKenzie et al., 2013). McKenzie et al. (2013) asserted that to reduce

75
threats to the quality of data , a statistical method can be employed to assess the internal
consistency for a measurement instrument .One such method often used, is the
Cronbach’s alpha reliability coefficient to estimate the instrument reliability rate. The
correlation coefficient (reliability coefficient) alpha Cronbach with a high level of
reliability preferably more than .70 must be computed (University of South Alabama, n.
d.) for a good reliability level. In fact, conducting a factorial analysis, the coefficient of
reliability can evaluate the instrument reliability level. According to Cronbach (1951)
reporting the coefficient alpha, Cronbach has become the most used measure of internal
consistency. It is convenient, simple, and can be computed in a multi-item scale
administration (McCrae et al., 2011). Nunnally and Bernstein (1994) noted that
coefficients often provide a good estimate of reliability as the main source of
measurement error for static constructs is the sampling of content ___ “should be applied
to all new measurement methods” (McCrae et al., 2011, Pp. 251-252). In addition to the
Cronbach’s alpha reliability coefficient, rater reliability and test-retest reliability can be
used to control the reliability of the measurement instrument (McKenzie et al., 2013).
As mentioned in the early section, prior to conducting the DHS surveys, to ensure
the instrumentation quality, the DHS program has examined and pretested through a pilot
study the questionnaires (ICF International, 2012a; 2012b). In fact, a pretest of the
questionnaire was conducted in few clusters not previously selected for the main survey
to assess the instruments (questionnaires) quality and ensure the understanding of the
translations by both the respondents and interviewers (ICF International, 2012 a).
Additionally, DHS Program continuously updates their data collection instruments and

76
methodology according to developments in international and national priorities, new
technologies, and ways to maximize quality results and efficiency (Measure Evaluation.
Org. n. d.).
Data Analysis Plan
Study Variables
As a scholar, one must be able to define not only the variables under investigation
but also, their operational definition aligned with the research questions and hypotheses
(Creswell, 2009).
Independent Variables (Exposures)
The main predictive factors are:
▪ Access to improved sanitation sources
▪ Access to improved water sources
▪ Adequate Hygiene
Below in a tabular format I described the variables and core questions from the
database.
Table 4.
Definition of Sanitation and Core Questions
Sanitation
Sanitation core questions
What kind of toilet facility do members of your household usually use?
Do you share this facility with others who are not members of your household?

77
With how many households do you share this facility?
The last time (Name of Child U5) passed stools, what was done to dispose of the stools?
MDG Categorization of Households
(2)
JMP
Disaggregated
Categorization of
Households
Underlying Questionnaire
Responses
Not using improved sanitation
open defecation
Unimproved
No facilities, bush or field,
open water bodies (open
defecation)
Flush or pour-flush to
elsewhere (that is, not to the
piped sewer system, septic
tank, or pit latrine)
Pit latrine without a slab, or
open pit Bucket
Hanging toilet or hanging
latrine
Shared use of a
Use of facilities listed below
facility otherwise
were shared by more than one
classified as household
‘improved’
Flush or pour-flush to a piped
sewer or septic tank or latrine
pit
Improved Ventilated improved pit (VIP)
Using improved sanitation
sanitation latrine
Pit latrine with slab
Composting toilet

78
Table 5.
Definition of water and core questions
Drinking Water
Drinking water core questions
What is the main source of drinking water for members of your household?
Where is that water source located?
How long does it take to go there, get water, and come back?
Who usually goes to this source to collect the water for your household?
Do you do anything to the water to make it safer to drink?
What do you usually do to make the water safer to drink?
MDG Categorization of
Households (2)
JMP Disaggregated
Categorization of
Households
Underlying Questionnaire
Responses
Not using an improved
drinking water source
Collection of water from a
surface water source
Surface water (river, dam, lake,
pond, stream, canal, irrigation
channel)
“Other unimproved
sources”
Unprotected dug well
Unprotected spring
Cart with small tank or drum
Tanker truck (3)
Bottled water where other water
source is classified as
unimproved (4)
Piped drinking water
into dwelling, plot, or
yard
Piped water into dwelling, yard,
or plot
Table 6.
Definition of Hygiene and Core Questions

79
Hygiene core question
Can you please show me where members of your household most often wash their hands? (Observe
presence of soap, water)
Do you have any soap or detergent (or other locally used cleansing agent) in your household for
washing hands?
MDG Categorization of
Households (2)
JMP Disaggregated
Categorization of Households
Underlying Questionnaire
Responses
Using adequate hygiene
Adequate hygiene supplies
Presence of soap and water for
handwashing
Not using adequate
hygiene
Inadequate hygiene supplies
Absence of soap, water, or both in
handwashing process
Water and sanitation quality are coded based on the sanitation scale suggested by
the WHO/UNICEF Joint Monitoring Program (JMP) as dichotomous improved or
unimproved sanitation and water (Fink et al., 2011).
From the Household data a binary ‘Water’ variable was created to denote
improved (coded 1) and unimproved code 2) sources. Improved water sources (classified
as standpipes or public taps, protected springs or rainwater collection, boreholes, or tube
wells, protected dug wells, piped water on-premises: Piped household water connection
located inside the user’s dwelling, plot, or yard).
Sanitation: Following the same rationale, toilet/sanitation will be categorized in
different presumed ‘quality’: 1) poor (no access to any toilet facilities), 2) intermediate
(indicates access to improved or basic latrine) and 3) high (indicates access to a flush
toilet) (Fink et al., 2011). Given the above I regrouped these categories in only 2
dichotomic levels coded as 1 (improved sanitation facility) and 2 (unimproved
sanitation).

80
Hygiene is grouped following this specification based on its definition
from
WHO/UNICEF Joint Monitoring Program (JMP). Variable for ‘Using adequate hygiene’
was based on adequate hygiene supplies, that is, presence of soap and water for
handwashing; while not using adequate hygiene implied absence of soap, water, or both
in the handwashing process. To construct this variable, all “No” responses to ‘Presence of
water at hand washing place’ were treated at inadequate hygiene, and additionally, if
water was present but “No cleansing agent observed”, these were also treated as
inadequate hygiene. In sum, I created new variables from the definition given and
grouped hygiene into 2 dichotomic categories , coded as 1 ( adequate hygiene) and 2 (
inadequate hygiene).
Hygiene categories
Using adequate hygiene
Adequate hygiene supplies
Presence of soap and water for handwashing
Not using adequate hygiene
Inadequate hygiene supplies
Absence of soap, water, or both in handwashing
process
Dependent Variables (Outcome Variable)
Under 5 mortality is the main outcome variable in this study. This is
selfexplanatory and it is the rate of death among children of the set age range. The
outcome variable is dichotomous and coded with child death (1= Death) or Alive (0
=Alive). As the characteristics and coding of the study variables are described, below I
discuss the protocol to access the DHS data.
Access to Secondary Data

81
In this study no data was collected because I used a secondary data, the DHS data.
However, I followed the protocol to get access to this data e.g., the IRB approval to
access secondary data. Therefore, I emailed, called, and presented the IRB approval
documents, along with the Data Use Agreement form to the responsible Agency (DHS
program) prior to the retrieval of the data. Once all documents were signed and agreed
upon, I got access to the DHS data electronically. As aforementioned, all the information
in the data was already cleaned and de-identified so that study participants’ names,
addresses, and other forms of contact information are available to users.
For the purpose of this study, I examined the effect of water, sanitation, and
hygiene on mortality among children under 5 in Côte D’Ivoire. As Smith and Firth (2011)
noted, prior to conduct a study, the investigator should make an adequate planning to
ensure the following: (1) how to retrieve and store the collected data; (2) how to
systematically code both interpretive and descriptive information during data analysis ;
and (3) how to develop a scholarly report containing a summary of the study results.
Following such steps may help readership to get an insight of the process and a better
understanding overall. And this resonates well with Nowell et al. (2017) views, according
to the authors, it is essential to clearly explain the process to the readership for instance,
how the data have been analyzed and/or what assumptions supported their analysis.
For this study purpose, I specifically examined to (a) what extent improved sanitation
sources affect the under 5 mortality among women 15-49 in Côte D’Ivoire; (b) to what
extent improved water sources affect the under 5e mortality among women 15-49 in Cote
D’Ivoire?; (c) to what extent hygiene affect the under 5 mortality among women 15-49 in

82
Cote D’Ivoire? , and lastly (d) to what extent improved water and sanitation sources, and
hygiene affect the under 5 mortality among women 15-49 in Cote D’Ivoire?
The DHS data are routinely captured, entered, cleaned, and coded with their own
specifications (Measure Evaluation. Org. n. d.; ICF International, 2012). I then retrieved
the pooled data and worked on the variables needed to address my research questions and
used the Statistical Program for Social Sciences (SPSS), IBM Corporation, Version 27 for
data analysis. SPSS is a software package that provides users with statistical analysis,
modeling, predictive, and survey research tools used for advanced research activities.
Firstly, I assessed the effect of each WaSH variable on the outcome variable, then I
measured the joint effect of the WaSH variables on U5MR. Secondly, I used survival
information within five years prior to the interview. I conducted a statistical analysis with
descriptive statistics (such as frequencies tables, percentages, and counts) about the
potential confounders by the survey year. Then, I computed the mortality rates associated
with both variables. In addition, I conducted multivariate analysis such as Cox
proportional hazard methods (CPH) which is also a survival analysis indeed. Prior to
running these statistics, I tested the proportionality assumption associated with the use of
the CPH method. Cox proportional model is effective in determining the hazard ratio
related to the under-five survival by controlling multiple covariates and confounders in
the model simultaneously (Forthofer et al., 2007). In sum, this analysis answered the
research questions aligned with the suggested hypotheses.
Statistical Analysis for Each Research Question/Hypothesis

83
This research focuses on the association between access WaSH on under-five
mortality. A multivariate analysis such as Cox proportional hazard survival analysis was
undertaken to examine the strength of the relationship between water, sanitation and
hygiene and the survival outcome (in terms of mortality) of the under-five children. To
examine the effect of the combined water and sanitation sources and hygiene on the
mortality among children below five, I conducted a multivariable analysis using Cox
proportional hazard regression model as a survival analysis. Not only each individual
variable was measured separately; but also, their cumulative effect was examined
simultaneously using this multivariate approach. Below, I provided the way I examined
the effect of the study variables and the outcome of interest. For the multivariable model,
a staged modeling technique was used, for instance, in the first stage, all the
demographic, socioeconomic, and maternal variables were entered into the baseline
multivariable model to assess their relationship with the study outcome (Mortality). A
stepwise backwards elimination process was conducted, and all variables significantly
associated with the study outcome variable at a 5% significance level were retained in the
model (model 1).
Research Question1(RQ1): To what extent does access to improved sanitation facilities
affect the under 5 mortalities among women 15-49 in Cote D’Ivoire while controlling for
demographic, socioeconomic, and maternal variables.
The null hypothesis (H01): There is no statistically significant difference in the
under 5 mortalities while controlling for demographic, socioeconomic, and maternal
variables among women 15-49 in Cote D’Ivoire with access to improved sanitation

84
facilities and those without.
The alternative hypothesis (HA1): There is no statistically significant difference
in the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
sanitation facilities and those without.
In this scenario, Cox proportional hazard regression model was conducted, and sanitation
facilities were independently examined with the socioeconomic ,demographic, and
maternal variables that were significantly associated with mortality, and those variables
with p-values < 0.05 will be retained (model 2).
Research Question 2 (RQ2): To what extent does access to improved water sources affect
the under 5 mortality among women 15-49 in Cote D’Ivoire while controlling for
demographic, socioeconomic, and maternal variables?
The null hypothesis (H02):There is no statistically significant difference in the
under 5e mortality while controlling for the demographic ,socioeconomic ,and maternal
variables among women 15-49 in Cote D’Ivoire with access to improved water sources
and those without.
The alternative hypothesis (HA2): There is a statistically significant difference in
the under 5 mortality while controlling for the demographic ,socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved water
sources and those without .
With regards to RQ2 also Cox proportional hazard regression model was used, and water
sources was independently examined with the socioeconomic, demographic, and

85
maternal variables that were significantly associated with mortality. As earlier, those
variables with p-values <0.05 will be retained (model 3).
Research Question 3(RQ3):To what extent does adequate hygiene affect the under 5e
mortality among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables ?
The null hypothesis (H03): There is no statistically significant difference in the
under 5 mortalities while controlling for the demographic, socioeconomic, and maternal
variables among women 15-49 in Cote D’Ivoire with adequate hygiene and those
without.
The alternative hypothesis (HA3): There is a statistically significant difference in
the under 5 mortality while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with adequate hygiene and
those without.
In the RQ3, Cox proportional hazard regression model was used with a similar
procedure above , so hygiene was independently examined with the socioeconomic ,
demographic, and maternal variables that were significantly associated with the mortality
outcomes. As before, those variables with p-values <0.05 will be retained (model 4).
Research Question 4 (RQ4): To what extent does access to improved water sources,
improved sanitation facilities, and adequate hygiene affect the under 5 mortality among
women 15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and
maternal variables?

86
The null hypothesis (H04): There is no statistically significant difference in the
under 5 mortalities while controlling for the demographic, socioeconomic, and maternal
variables among women 15-49 in Cote D’Ivoire with access to improved water sources,
improved sanitation facilities, and adequate hygiene and those without.
The alternative hypothesis (HA4): There is a statistically significant difference in
the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved water
sources, improved sanitation facilities, and adequate hygiene and those without.
Similarly, to the research questions above, for RQ4 also, I conducted cox proportional
hazard regression models. In the last stage (model 5) all three independent variables
(water , sanitation, and hygiene) were simultaneously examined with all the variables
entered into model 1, and those variables with p-values <0.05 will be retained in the final
model (model 5).
The estimates in the Cox proportional hazard model are the hazard ratios (HR)
and their 95% confidence intervals obtained from the adjusted Cox proportional hazard
models was used to assess the simultaneous effect of water sources, sanitation sources,
and hygiene on the under 5 mortalities. It automatically controlled for all confounding
and interacting variables into the model that also affect the outcome variable of this study.
Prior to running these statistics, I assessed the proportionality assumption associated with
the use of the CPH method. Cox proportional model was effective in determining the
hazard ratio related to the under-five survival by controlling multiple covariates and/or

87
confounders in the model simultaneously (Forthofer et al., 2007). In sum, this analysis
answered the research questions aligned with the suggested hypotheses.
Cox proportionality is also known as a semi-parametric method. According to
Sullivan (2012), in CPH hazards ratio is the measure of effect and represents the risk or
probability of suffering the event of interest, “conditional on the fact that the participant
has survived up to a specific time” (p. 260). Cox proportional hazard (CPH) method
provides the value of the Hazard Ratio which is a proxy for the Odds ratio (in the logistic
regression model) (Forthofer et al., 2007). CPH models can also distinguish individual
contributions of covariates on survival. CPH model is an appealing analytic approach
because it is both flexible and powerful (Spruance et al., 2004). Moreover, using SPSS, I
did an adjustment of the cluster sampling and estimated standard errors. As mentioned in
the section above, I conducted correction tests to minimize information bias.
Furthermore, comparing the unadjusted HR and the adjusted HR can help to assess the
magnitude of potential effect modification (or an interaction effect) and report them.
Strengths and Limits
The study method is an observational quantitative design, also known as
correlational. Most particularly, cross-sectional analytical design to examine multiple
factors including WaSH variables on U5MR. As the relationship is only correlational, no
causal link can be determined in such designs (Frankfort-Nachmias, Nachmias, &
DeWaard, 2015). This design is relatively quick and easy to conduct, data on all variables
are collected once. One of the strengths of this design is the fact that it provides a
snapshot of events or disease frequency and distribution at a given point in time, unlike

88
experimental designs where causality can be assessed through experiment (by comparing
control and experimental groups), this is impossible in observational studies such as
cross-sectional designs (Forthofer et al., 2007). Another strength of cross-sectional
studies is that the study participants do not need to follow any experimental protocol with
exposure to an intervention that can be ethically challenging (Mann, 2012).
Additionally, in cross-sectional design studies, there is no need to form groups in
control versus experimental groups. Hence, the same data source is generally sufficient to
make inferences and assess the relationship between the study variables that may yield
many possible outcomes as well. Cross-sectional is associated with a single data
collection point, relatively inexpensive yet can be a source of possible spurious
associations between the study variables. The cross-sectional design is also useful to
provide evidence-based information for decision making, planning, and resource
allocation for prevention and healthcare (Health Knowledge, n. d.). Moreover, using this
design, a large sample size can be drawn (i.e., the DHS household surveys are between
5,000 and 30,000), leading to a higher external validity and power for the study results
(Forthofer et al., 2007; Frankfort-Nachmias et al., 2008).
Using multi-stage cluster sampling methodology is cost-effective, less time
consuming, and appropriate with sampling frames readily available at the level of the
cluster. This design is relevant for institutional surveys (Johns Hopkins Bloomberg
School of Public Health, 2009). With regards to the strength of the instrumentation, the
DHS questionnaires have a high level of reliability, the surveys have large sample sizes
(between 5,000 and 30,000 households) and are routinely undertaken every 5 years to

89
allow comparisons over time (ICF International, 2012b). One great strength of DHS data
is that multiple factors can be examined with child mortality. However, secondary data
with the cross-sectional design is not suitable to ascertain a cause-and-effect relationship
between variables under study (Frankfort-Nachmias et al., 2008; Szklo et al., 2014).
With regards to the DHS data, Asaolu et al. (2016) noted that the cross-sectional
drawn from DHS has some limitations including recall bias led by inaccurate reporting of
event timing or the level of underreporting. One strength of the data analysis approach is
the use of the CPH method, a powerful and flexible (Spruance et al., 2004) method to
simultaneously control multiple covariates and confounders in the model (Forthofer et al.,
2007). In addition, through SPSS I can make the necessary adjustments to cluster
sampling and measure standard errors. Another strength is the restriction of the analysis
to the most recent births within 5 years prior to each survey to minimize potential recall
bias on death and birth dates reported in the survey data. Additionally, appropriate
adjustments for sampling design, sampling weight, and the high response rate (about
95%) to the survey are key strengths for the DHS data (Ezeh et al., 2014). Despite
countless advantages of the design, the methodology, and the measurement tool; the risk
of spuriousness led by random errors, bias, confounding, and the interaction effect may
still trigger the study validity and reliability. Thereby, interested researchers using this
data must effectively assess, control, and report these issues.
Threats to Validity

90
McKenzie et al. (2013) suggested that “it is of vital importance that planners and
evaluators make sure that the data they collect are accurate, reliable, valid, fair and
unbiased” (p.117). Similarly, Issel (2009) emphasized that because threat to data quality
is present regardless of how effective data has been collected; therefore, it is essential to
minimize them to improve data quality. The quality (validity and reliability) of the
measurement instrument is also essential, a poor instrumentation would more likely
trigger the quality of the data gained from that instrument. As aforementioned in the early
section, prior to conducting the DHS surveys, to ensure the instrumentation quality, the
DHS program has examined and pretested the measurement tool through a pilot study
(ICF International, 2012a; 2012b). In fact, a pretest of the questionnaire was conducted in
few clusters not previously selected for the main survey to assess the instruments
(questionnaires) quality and ensure the understanding of the translations by both the
respondents and interviewers (ICF International, 2012 a). Additionally, Issel (2009)
asserted that during the collection of data “the observation should be as unobtrusive as
possible” (p.123) and ensuring that sensitive information be held confidentially and
anonymously (McKenzie et al., 2013). Fortunately, these ethical protocols have been
followed by the DHS program during data collection as amply discussed earlier in the
data collection section (ICF International, 2012a, Measure Evaluation. Org. n. d.). The
following are potential elements (i.e., biases, confounders, and interactions effect) that
may trigger data quality.
Selection Biases

91
The representativeness and generalization of the research findings are related to
how well the target population was sampled. Thus, it is important to ensure an effective
sample design and an adequate sample size aligned with the research question and
objectives (Frankfort-Nachmias et al., 2008; Forthofer et al., 2007). Selection bias occurs
when selecting study participants or their likelihood of being retained in the study
induces different results if the entire target population were considered (Boston
University School of Public Health, n. d.). When the sampling is non-representative of
the exposure-outcome distributions in the overall population, this will distort (selection
bias) the measures of association (Boston University School of Public Health, n. d.).
Szklo et al. (2014) defines selection bias as a systematic error while conducting or
designing a study and it is induced by flaws either in the selection method used for study
participants or in the procedures to collect exposure and /or disease data: consequently,”
the observed study results will tend to be different from the true results” (p. 100). This
bias tends to influence the probabilities of inclusion of the study participants in the study
sample based upon relevant study characteristics e.g., the outcome and exposure (Szklo et
al., 2014). Not addressing these biases may lead to a distortion of the study validity and
power by extrapolating (or overestimating) or underestimating the true strength of the
association between predictors and dependent variables (Frankfort-Nachmias et al, 2008).
Not addressing this will finally bias point estimates and standard errors leading to
incorrect inferences (Bell et al., 2012). Bell and colleague’s perspective clearly elucidated
the importance of weighting using this descriptive argument while all these elements
cited above must be considered with complex surveys data to minimize bias(s) that may

92
arise from differences in designs, sampling methods, and the measurement approach used
for these data collections.
In fact, selection bias can occur in my study both at the design stage, if the
adequate sampling design and sample size associated with research questions and
objectives were done ineffectively. Because I am already aware of potential biases, I
carefully examined the study design and conducted the study to minimize any internal
and external validity concerns including selection bias and other biases.
Strategies to Minimize Selection Bias in his Study
According to Szklo et al. (2014), quality control and quality assurance are
essential to minimize bias and some specific ways to address this bias include ensuring a
detailed protocol design and developing appropriate data collection tools and procedures.
Moreover, training and certifying the field staff, doing a pilot study, and pre-testing
before full implementation (Szklo & Nieto, 2014) are important steps to minimize
selection bias at the early stage. Thus, I did a priori sample size calculation based on the
study design and all the parameters needed for this computation. Because my study is a
secondary data analysis, it implies that the data has been previously collected by the DHS
Agency with a specific sampling design, data collection tool, and strategies. The DHS
data used a probability sampling to select the study population. This sampling method
provides the statistical basis of the representativeness of the sample drawn from the target
population. A probability sampling assumes that everyone (from the target population)
will have the same likelihood for selection. The randomness of this design will increase
the representativeness of the survey population (McKenzie, Neiger, & Thackeray, 2013).

93
While a non-probability sampling cannot achieve randomness (Issel, 2009), the
assumption is that the data collectors have considered that there is a minimal or no
difference between participants in the program and those who are not. Fortunately, the
DHS data has a huge size which may more likely increase the external validity of this
study. Another way to minimize selection bias is before data collection which is not
applied in the current scenario because data is previously collected) prior to the sampling
at the design stage could be matching and sensitivity analysis (Ha et al., 2016). For
instance, matching socio-demographics and economic characteristics of the potential
study participants can help to minimize selection bias.
Another approach to address selection bias is using weighting adjustments. For
instance, weighting can compensate for biased estimators induced by survey nonresponse
(Pike, 2008). Weighting can help to determine sub-groups in the sample observation of
the collected data as well as assess variations and characteristics of these subgroups in the
collated data. Using weighing can correct survey data addressing potential biases that
may arise without adjustment. Large nationally representative health surveys data differ
from simple random sampling surveys in four elements (Bell, Onwuegbuzie, Ferron, Jiao,
Hibbard, & Kromrey, 2012):
● The unequal probabilities of selection and oversampling of certain
populations subgroups generally use sample design in surveys to ensure
accurate precision of parameters estimated.
● “Multistage sampling results in clustered observations (where variance
among units within each cluster is less than the variance among units in
general)” (p.3).

94
● The issue with sampling stratification, although it may ensure adequate
representative sampling pertaining to the stratified variable(s), this may
also lead to inaccurate estimates of the variance.
● And lastly, the nonresponse unit and other poststratification corrections or
adjustments are employed to the sample to allow unbiased estimates (Bell
et al., 2012).
Information Biases
There are two main types of biases: Selection bias and information bias (Szklo et
al., 2014). Information bias in an epidemiologic study is induced by either imperfect
definition of the study variables or flawed data collection procedures. These errors may
lead to misclassification of exposure, or an outcome status for a substantial proportion of
participants (Szklo et al., 2014). There are differential and non- differential
misclassification. In general, misclassification comes from 1) incomplete medical
records, 2) errors in recording, 3) records misinterpretation or errors in records, e.g.,
incomplete filling of questionnaires or incorrect disease codes (Statistics How To, 2017).
Given the above and because data was already collected (secondary data), I think
my research may have several types of informational bias. For instance, information bias
due to incorrect completion of the household questionnaires, sensitive questions may
have triggered reluctance to correctly give the correct response to these sensitive
questions. In addition, recall bias may have occurred due to a long time between
interviews (as these DHS surveys are conducted every 5 years). Lastly, respondents may

95
have faced challenges to provide accurate information due to memory gaps about the
under 5 birth history and parental financial status.
Moreover, there might be differential misclassification between groups, those
with more advantageous socioeconomic status have more access to better conditions
(water, sanitation facilities, and hygiene) as compared to counterparts with lower SES.
This context may lead to differential exposure bias; subsequently, a differential outcome
as the combined effect of the exposure (i.e., better sanitation, better water facilities, and
hygiene) as well. In addition, some errors in records can lead to informational bias.
Furthermore, observer bias due to the presence of the interviewer during the interview,
depending on the level of social desirability needed of the respondents. Lastly, non-
response may have occurred as well.
Other challenges associated with reliable and correct data collection for the DHS
surveys may be the lack of comfort of respondents to disclose sensitive information. How
perceived confidential and anonymous questions were handled or asked? This could also
increase social desirability bias and recall bias in addition to the choice of respondents (in
general, the head of the household responds to the questionnaire). However, it is not
evident that the head always has accurate information related to the family assets. So, it is
essential to select the respondents based on their level of knowledge of the household
source of finance.
In the DHS data, the measurement of socioeconomic position (SEP) and the
adequate data collection instruments—differ significantly between low- and high-income
nations (Howe et al., 2012). Unfortunately, DHS data do not have economic parameters

96
(i.e., income or consumption expenditure); therefore, assets, housing characteristics, and
access to basic sources (i.e., sanitation, drinking water, and electricity) are used as a
proxy (Howe et al., 2012).
Strategies to Minimize Information Bias
Ideally, it is more effective to assess and minimize information bias through
various approaches (i.e., during the design and data analysis stage). These include data
quality control and relevant statistical analysis. Quality assurance before data collection is
related to standardizing procedures and can prevent or at least minimize'' systematic or
random errors in collecting and analyzing data” (Szklo et al., 2014, p. 313). In contrast,
quality control is done after data collection and is fundamental as a remedial action aimed
at minimizing bias and reliability problems (Szklo et al., 2014). In the current study,
because the data was already collected through DHS household surveys, the quality
assurance was seemingly done prior to data collection. Szklo et al. suggested that kappa
statistics at the analysis stage be used to explore the likelihood of differential exposure
misclassification bias, and the Bland-Altman plot for concise summary measures
optionally to minimize the bias.
Confounding Variables
The most effective approach to minimize spurious factors including confounders,
it is critical to carefully do a study plan, design, and beyond; as well as the use of
statistical analysis and stratification, thereafter to control the remaining confounders
(Sullivan, 2012). Unless some of the variables cannot be controlled e.g., residual
97
confounders, however, with large sample size and randomization such issues could be
minimized in general.
Confounding variables: Household wealth index, spouse/paternal level of
education, place of residence , maternal education , mother work status, number of
residents in the household over the age of five, father work status, presence of child
health card with the mother, number of household members, place of residence, religion,
matrimonial status, regions of residence, gender of woman’s child, mother age at
childbirth. The assets followed the DHS data e.g., car, phone, radio, fridge, type of floor
material used in rooms, television, electricity, bicycle, and motorcycle. In this
questionnaire, the household wealth index was grouped as richer, poorer, richest, middle,
and poorest. For more convenient analysis, I re-categorized the household wealth index
into) 1) poorest households and2) Non poor households. Table 7 is a sample of the type of
numerical descriptive statistical analysis conducted. Lastly, the level of U5MR was
assessed as the outcome variable, while controlling for confounding and interaction
effects simultaneously.
Table 7.
Mother Caregivers Socio-demographic Characteristics of the Children less than Five years
≤29
Age (years)
≥ 30
Male
Gender of woman’s child
Female
Presence of child
Yes/No
Variables Definition
Categorization/groups
Frequenc
y
Percent

98
health card with the
mother
Poor
Middle
Rich
Matrimonial Status
Single
Married
Divorced/separated/widow
/
Polygamous
Monogamous
Single parenthood
Religion
Christianity
Islam
Traditional
Others
Regions of Residence
Place of Residence
Centre
Centre East
Centre North
Centre West
North
Northeast
Northwest
West
South
Southwest
City of Abidjan
Rural
Urban
1 under 5 child
Number of under-five
children caring for
≥ 2 under 5 children
Number of household
members
≤ 4
≥ 5
Number of bedrooms
occupied
≤ 3
≥ 4

99
Maternal level of education
No Formal
Primary
Secondary
Tertiary
Others
Spouse/ paternal level of
education
No Formal
Primary
Secondary
Tertiary
Others
Household wealth Index
Respondents’ occupation
1. poor households
2. middle households
3. rich households
Business/Commerce Civil
Service
semi -skilled
Others
Controlling Confounding Variables
DHS data is a secondary source of data so I do not have control of the
confounding variables at the designing stage because the study was already designed and
data was already gathered, so spurious factors e.g., effect modifiers and confounders
could be addressed through statistical analysis. The estimates in the Cox proportional
hazard model are the hazard ratios (HR) and their 95% confidence intervals obtained
from the adjusted Cox proportional hazard models was used to assess the effect of the
combined effect of water sources, sanitation sources, and hygiene on the U5M. Cox
proportional regression automatically controlled for all confounding and interacting
variables into the model that also affect the outcome variable of this study. This section is

100
related to the statistical analysis plan and methods, including descriptive statistics (such
as frequencies) about the potential confounders, then the computation of the mortality
rates associated with both variables (i.e., water sources, sanitation facilities, and hygiene).
In the analysis stage, I used multiple variates method to evaluate WaSH variables and
their influence on U5MR using survival analysis such as Cox proportional hazard method
(Ezeh et al., 2014).The key interesting fact using Cox proportional model is its powerful
capability to determine the hazard ratio associated with the under 5 survival while
controlling multiple covariates and/or confounders in the model simultaneously
(Forthofer et al., 2007). Conclusively, observational research is susceptible to chance,
bias, and confounding effects, therefore, these elements must be taken into consideration
at the design and analysis stages to minimize their distortion in the study results (Health
Knowledge, 2011).
Statistical Limitations
Even though this study might have a great deal of external validity (mainly due to
the huge sample size) and power, limitations inherent to the study design must be
considered. One of the main limitations is the fact that causality cannot be ascertained in
a cross-sectional design, because no temporal relationship between exposure (water,
sanitation, and hygiene) and outcome (under 5 mortality) can be inferred from this
analysis. Often cross-sectional studies estimate prevalent rather than incident cases; yet
the data will always reflect determinants of survival as well as etiology (Health
Knowledge, n. d.).

101
Social Change Implications
Practical Contributions of this Study for Public Health and Epidemiology
In public health, programmatic, advocacy, and health policy perspective, the
assessment of the impact of water and sanitation program will provide tangible and
substantial evidence to inform decision making for planning and prevention through
designing effective upstream population-based strategies to mitigate or minimize the
problem vulnerable individuals face in Cote D’Ivoire and elsewhere. Evidence-based data
from this study can also guide program planners, public health practitioners, researchers,
and funders for effective decision making. In addition, this study could serve to guide and
advocate more resources for the program and help the affected community in Cote
D’Ivoire and beyond. Lastly, from an epidemiological standpoint, the examination of
multiple risk factors associated with child mortality in this cross-sectional study could
provide more insight into the multifactorial determinants of child mortality. As well as to
guide for prioritization and prevention measures for the population at risk to empower
them e.g., improve well -being, reduce related morbidity and mortality of the target
population.
The potential social change implication includes the use of health education and
promotion to sensitize the local community to adopt preventive behaviors (i.e., proper
hygiene attitude; provide education programs; promote availability and access to clean
water; and proper sanitation facilities). As aforementioned, all this would gradually
impact the community well-being, quality of life, and life expectancy. In a programmatic
standpoint, insights from this study may guide and frame prospective program planning,

102
prevention, advocacy, and resources allocation (Parker, & Thorson, 2009; Resnick et al.,
2013).
Ethical Procedures
Like traditional biomedical research, compliance with the ethics guidelines using
de-identified data not only can provide benefits, but also, minimize issues with privacy,
confidentiality, and risks. In this research study, I used DHS data to examine the strength
of the association between child survival and access to WaSH variables. First, I followed
the DHS protocol for data granting and retrieval from the appropriate Agency. DHS data
is a nationally representative household survey mainly funded by “the United States
Agency for International Development and implemented by Macro International in
collaboration with national statistical agencies (Fink et al., 2011).
I presented the IRB approval documents, along with the Data Use Agreement
form, to the Agency prior to retrieval of the data. Once all documents were signed and
agreed upon, I was allowed access to the DHS data on September 4th, 2020 (IRB number
: 09-04-20-0296262). Before data collection by the DHS Agencies, various ethical
procedures were applied and followed to ensure the privacy, autonomy, and
confidentiality of the respondents (ICF International, 2012a, Measure Evaluation. Org. n.
d.). Confidentiality is a major concern for DHS, in fact, the DHS surveys are anonymous
surveys which do not allow any potential identification of any single individual or
household in the data file. Confidentiality is also a key factor influencing response rate to
sensitive questions pertaining to partners and sexual activity. For instance, in surveys that
include HIV testing DHS policy requires that household codes and PSU be scrambled in

103
the final data to further anonymize the data and destroy the original sample list (ICF
International, 2012a).
Furthermore, the household questionnaire in the DHS survey starts with an
introductive message explaining the “Informed consent” and the objective of the
interview before agreement and signing. In addition, the questionnaires were filled
confidentially and anonymously with the incorporation of the final deidentified and
aggregated data to comply with ethical protocols (ICF International, 2012a) including
confidentiality, anonymity, privacy, and respect of human subjects used as study
participants. This resonates well with Rothstein (2015) assertion that loss of privacy may
lead to both intangible and tangible harms. Careful consideration of legal and ethical
issues is key while doing research with humans’ participants. Doing so could facilitate
effective implementation, planning, and enhancement of various public health programs
and research activities.
Summary
The under 5 mortalities have declined to 39 -50 percent per 1,000 live births (UN
IGME & UN MMEIG, 2019). Despite remarkable progress in child survival overall, huge
disparities still appear between regions. Sub-Saharan Africa (SSA) still lag behind
expectations (UN IGME & UN MMEIG, 2019). The lack of or limited WaSH quality and
access expose millions of children to morbidities associated with WaSH and subsequently
leading to preventable death. About 800 million of children die daily from diarrhea and
other illnesses mainly led by lack and/or improper sanitation and water sources (UNICEF
Côte D’Ivoire, n. d). Understanding how WaSH influences childhood health (i.e., U5MR)

104
are critical to minimize its burden; hence, reducing case-specific morbidity and mortality
among these children. This study seeks to better understand the risk exposure faced by
children below five in Cote D’Ivoire and its linkage to the high U5MR. The overall goal
of this study was to specifically explore the magnitude of the relationship between access
to improved WaSH and mortality in children less than 5 among women 15-49 years old
in Cote D’Ivoire, using all available and relevant Cote D’Ivoire DHS data from 2005-
2020. This study expects to contribute to child survival literature by examining how
WaSH affects children’s mortality. In this research study, I expect to provide an insight
into the current strength of the association between U5MR and access to water,
sanitation, and hygiene using pooled Cote D’Ivoire DHS data. The section above
described the study design and rationale; the research methodology; the study population;
the setting; the recruitment strategy; power analysis and sample size; the sampling
method; the data collection tools; definition of the study variables; the DHS data and
protocol to access; and statistical analysis plan. Moreover, chapter 3 introduced and
addressed potential threats to the study validity and provided a thorough explanation of
related ethical procedures. In Chapter 4, I present the results of the study.

105
Chapter 4: Results
The purpose of this study was to examine the magnitude of the association
between access to WaSH variables and the under 5 mortality rates among women 15-49
in Cote D’Ivoire. This research tried to uncover the extent to which WaSH affects
mortality in this age group. I design the following research questions and related
hypotheses to guide this research:
Research Questions and Hypotheses
RQ1: To what extent does access to improved sanitation facilities affect the under-5
mortality among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables?
H01: There is no statistically significant difference in the under-5 mortality while
controlling for demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved sanitation facilities and
those without.
HA1: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved sanitation facilities and
those without.
RQ2: To what extent does access to improved water sources affect the under-5 mortality
among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables?

106
H02: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources and those
without.
HA2: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources and those
without.
RQ3: To what extent does adequate hygiene affect the under-5 mortality among women
15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and maternal
variables?
H03: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among women
15-49 in Cote D’Ivoire with adequate hygiene and those without. HA3: There is a
statistically significant difference in the under-5 mortality while controlling for the
demographic, socioeconomic, and maternal variables among women 15-49 in Cote
D’Ivoire with adequate hygiene and those without. RQ4: To what extent does access to
improved water sources, improved sanitation facilities, and adequate hygiene affect the
under-5 mortality among women 15-49 in Cote
D’Ivoire while controlling for demographic, socioeconomic, and maternal variables?
H04: There is no statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among

107
women 15-49 in Cote D’Ivoire with access to improved water sources, improved
sanitation facilities, and adequate hygiene and those without.
HA4: There is a statistically significant difference in the under-5 mortality while
controlling for the demographic, socioeconomic, and maternal variables among
women 15-49 in Cote D’Ivoire with access to improved water sources, improved
sanitation facilities, and adequate hygiene and those without.
Data Collection
My research proposal was approved by Walden University IRB (09-04-
200296262), and the protocol for data access was granted on September 4th, 2020. I
therefore retrieved the DHS datasets and did not find any major discrepancy in the plan I
suggested earlier on Chapter 3. I conducted data quality for completeness, accuracy, and
consistency of the data set so that I could address missing data issues in the data set. To
examine the relationship between access to WaSH variables on U5MR, I used the Cote
D’Ivoire DHS data containing the full birth histories of the exposed children, WaSH
information, and several potential exposure factors expected to be examined.
For this study, I used the household questionnaire and information about WaSH
variables and other confounding variables were examined and measured. The birth
history contains information on child death, date of birth, gender, child survival status
(alive or dead), and child age at death. The DHS is an ongoing surveillance and
monitoring system to collect information in the household every 5 years across countries
worldwide (Demographic and Health Survey, 2018). The methodology used for data
collection involves trained enumerators conducting interviews using standardized

108
questionnaire instruments to eligible participants selected through a scientific sampling
design (Measure Evaluation.org., n.d., p. 59).
In this study, women aged between 15 to 49 years, with children under the
age of 5 who are dead or alive, were the target population. The data used for this
study were from the children’s module, woman’s module, and household module.
As Fink et al. (2011) noted, one of the main advantages of DHS data is the fact that
it enables investigators to look at child mortality and many other factors associated
with child mortality including socioeconomic factors, demographic characteristics,
and other comorbidities.
Descriptive Statistics
As Trochim (2006) noted, descriptive statistics explain simple characteristics of
quantitative data including variances, average, and sum (Frankfort-Nachmias &
LeonGuerrero, 2015). I conducted descriptive statistics such as counts, frequencies, and
percentages for the independent WaSH variables. I also conducted descriptive statistics
on selected demographic, socio- economic, and maternal characteristics of the target
population. Table 8 below shows the characteristics of children and their mothers enrolled
in the study. A total of 7,776 children under 5 years old were enrolled in this study. The
majority (53.6%) of them were 12-59 months old, followed by the 0-28 days (24.6%)
neonatal, and 1-11 months/post-neonatal (21.8%). The vast majority (83%) had a birth
card, and 70.8% received mother breast milk for at least 6 months. Most (58.2%) of the
mothers enrolled were young and under 30 years old. More than half (67.7%) of the

109
mothers did not have a formal education, and the majority of them (85.5) were living
with a male partner.
Table 8.
Characteristics of Children and Mothers Enrolled in the Study (N=7,776)
Gender of child
Female 49.5% (3852)
Male 50.5% (3924)
Child age group
0-59 months 91.2% (7093)
0–28 days/neonatal 24.6% (1910)
1-11 months/post-neonatal 21.8% (1695)
12–59 months/child 53.6% (4171)
Single birth 95.4% (7417)
Multiple births 4.6% (359)
Child has a birth card 83% (6420)
Child has no birth card 17% (1317)
Currently breastfeeding 33.8% (2597)
Not breastfeeding 66.2% (5091)
Breastfeeding >=6 months 70.8% (1838)
Breastfeeding <6 months 29.2% (759)
Weight at birth/recall
Not weighted 38.1% (2962)
From written card 39.3% (3056)
From mother`s recall 17.9% (1391)
Don`t know 0.6% (43)
Special answers 4.2% (324)
Birthweight average or larger 85.6% (3807)
Small or very small birth weight 14.4% (640)
Mother > 29 years 41.8% (3247)
Mother ≤29 years 58.2% (4529)
Mother education status
Some education 32.3% (2515)
No education 67.7% (5261)
Mother employment status
Working 71.6% (5565)
Characteristics
Frequency % (N=7,776)

110
Not working 28.4% (2211)
Mother husband or partner status
With a partner 85.5% (6648)
Without a partner 14.5% (1128)
Husband/partner education status
Husband/partner education status
Some education 34.5% (2686)
No education 62.3% (4842)
Missing information 3.2% (248)
Number of under 5 cared for
2 or more under 5 67.4% (5242)
0 or 1 under 5 children 32.6% (2534)
Mother religion
Muslim 45.7% (3548)
Catholic 16.1% (1245)
Methodist 1.9% (147)
Evangelical 15.2% (1182)
Other Christian 3.7% (290)
Animist 3.9% (300)
No religion 12.4% (965)
Other 1% (79)
Type of Water Sanitation Available in Households Where Children Lived
Table 9 describes the type of water sanitation available in households where
children lived. Less than a third (19.8%) of surveyed households had access to piped
water at home. Only 18.2% of the children lived in a household with flush toilets of
different categories. More than a third (34.4%) of these household members did not have
access to toilets in their households. About 47.4% of the households had water and
handwashing items present at the time of the survey.
Table 9.

111
Water and Sanitation Available in Households Where Children Lived
Household (N=9,679)
Characteristics
% N
Source of drinking water
Piped into dwelling
10.0%
923
Piped to yard/plot
20.0%
1,957
Public tap/standpipe
17.0%
1,616
Tube well or borehole
15.0%
1,443
Protected well
17.0%
1,661
Unprotected well
12.0%
1,202
Protected spring
0.5%
47
Unprotected spring
3.0%
256
River/dam/lake/ponds/stream/canal/ irrigation
channel
5.0%
461
Tanker truck
0.0%
2
Cart with small tank
0.0%
3
Bottled water
0.0%
29
Other
1.0%
79
Type of toilet facility in household
Flush to piped sewer system
5.1%
490
Flush to septic tank
10.2%
989
Flush to pit latrine
2.8%
271
Flush to somewhere else
0.1%
10
Flush, don't know where
0.0%
4
Ventilated Improved Pit latrine (VIP)
0.4%
38
Pit latrine with slab
26.9%
2,600
Pit latrine without slab/open pit
19.7%
1,905
Other type of toilets
0.3%
27
No facility/bush/field
34.4%
3,330
Water and handwashing items present
47.4%
4,585
112
I created “mortality age groups” as follows: 0-28 days (neo-natal), 1-11 months
(post neonatal), and 12-59 months (child). Table 10 describes the characteristics of the
children alive and those who died before reaching 5 years. The vast majority of the
children were alive (91.2%; 7,093/7,776). Among the children alive, 50.6% were female,
and among the 683 children who died, 61.6% were male. Out of the children alive, 57.3%
(4,061/7,093) were in the age group 12-59 months. The vast majority of the
women/mothers didn’t receive formal education, other characteristics are detailed in
Table 10.
Table 10.
Characteristics of Under-5 Status (Alive or Dead) by Demographic and Maternal
Factors
Characteristics
Child status
Child alive
(N=7093)
Child died
(N=683)
Total (N=7776)
% (n)
Proportion
Proportion
50.6%
Female
(3590)
38.4% (262)
49.5% (3852)
Male
49.4%
(3503)
61.6% (421)
50.5% (3924)
0–28 days/ neonatal
22.8%
(1615)
43.2% (295)
24.6% (1910)
1-11 months/ postneonatal
20% (1417)
40.7% (278)
21.8% (1695)
12–59 months/ child
57.3%
(4061)
16.1% (110)
53.6% (4171)
Working
71% (5036)
77.5% (529)
71.6% (5565)
Not working
29% (2057)
22.5% (154)
28.4% (2211)
Husband/partner
education status
Some education
36% (2472)
32.5% (214)
35.7% (2686)
No education
64% (4398)
67.5% (444)
64.3% (4842)

113
Some education
32.8%
(2324)
28% (191)
32.3% (2515)
No education
67.2%
(4769)
72% (492)
67.7% (5261)
Mother husband or partner
status
With a partner
85.4%
(6058)
86.4% (590)
85.5% (6648)
Without a partner
14.6%
13.6% (93)
14.5% (1128)
(1035)
Mother > 29 years
41.3%
(2932)
46.1% (315)
41.8% (3247)
Mother ≤29 years
58.7%
(4161)
53.9% (368)
58.2% (4529)
Religion
Muslim
45.5%
(3219)
48.2% (320)
45.7% (3548)
Catholic
16.2%
(1143)
14.9% (102)
16.1% (1245)
Methodist
2% (138)
1.3% (9)
1.9% (147)
Evangelical
15.4%
(1089)
13.6% (93)
15.2% (1182)
Other Christian
3.7% (265)
3.7% (25)
3.7% (290)
Animist
3.8% (270)
4.4% (30)
3.9% (300)
No religion
12.4% (878)
12.7% (87)
12.4% (965)
Other
1% (71)
1.2% (8)
1% (79)
Child has a birth card
91% (6420)
0.00%
83% (6420)
Child has no birth card
9% (634)
100% (683)
17% (1317)
Number of under 5 cared for
2 or more under 5s
69.4%
(4919)
47.3% (323)
67.4% (5242)
1 or 0 under 5 children
30.6%
(2174)
52.7% (360)
32.6% (2534)
Currently breastfeeding
36.9%
(2597)
0.00%
33.8% (2597)
Not breastfeeding
63.1%
(4432)
100% (659/659)
66.2% (5091)
Weight at birth/recall
Not weighted
37.1%
(2635)
47.9% (327)
38.1% (2962)
From written card
41.5%
(2942)
16.7% (114)
39.3% (3056)
From mother’s recall
17.4%
(1234)
23% (157)
17.9% (1391)
Don’t know
0.4% (30)
1.9% (13)
0.6% (43)
Special answers
3.6% (252)
10.5% (72)
4.2% (324)
Mother’s perceived birth size

114
Birth weight average or
larger
86.6%
(3615)
70.8%
(192/271)
85.6% (3807)
Small or very small
13.4% (561)
29.2% (79/271)
14.4% (640)
birth weight
The comparisons between child status (alive/dead) and a number of variables
were described by type of population and related distribution. These variables were
grouped in three categories: socio-demographic factors, household socio-economic
factors, and mother’s characteristics (respectively in Tables 11 & 12). For example, Table
11 shows the relationship between socio-demographic factors and under 5 survival versus
death. Table 12 shows the household socio-economic distribution and mothers’
characteristics with under 5 survival/versus death. The factors significantly associated
with child survival included living in a household with improved sanitation facilities,
with 2-4 siblings, being a female child, and or living in the Western region of the country
(Table 11). In Table 11, the frequency of each variable in relationship with children
mortality versus survival is reported.
● Poorest households Nonpoor households (45.2%) versus Poorest 40 percent of
households (54.8%)
● Male headed households have a higher under-five mortality (86.2%) versus
women Female headed households (13.8%).
Table 11.
Socio Demographic Factors and Under-five Survival Vs Mortality
Characteristics
Child Status

115
Child Alive
Child Died
Total
95.0% CI
p-
n=7,09
%
3
n=683 %
N
%
Lower Upper
value
Female
headed
households
Male headed
household
Female
headed
household
6059
1034
85.4%
14.6%
589
94
86.2%
13.8%
6648
1128
85.5%
14.5%
0.78
Ref
1.26
0.937
Electricity
status
Electricity
No electricity
3355
3738
47.3%
52.7%
280
403
41.0%
59.0%
3635
4141
46.7%
53.3%
0.64
Ref
1.04
0.099
Radio
Radio owned
4109
57.9%
370
54.2%
4479
57.6%
0.69
0.97
0.023
No radio
2984
42.1%
313
45.8%
3297
42.4%
Ref
Television
Television owned
2703
38.1%
228
33.4%
2931
37.7%
0.75
1.22
0.713
No television
4390
61.9%
455
66.6%
4845
62.3%
Ref
Refrigerato
r
Refrigerator
owned No
refrigerator
653
6440
9.2%
90.8%
56
627
8.2%
91.8%
709
7067
9.1%
90.9%
0.81
Ref
1.53
0.515
Bicycle
Bicycle owned
3677
51.8%
404
59.2%
4081
52.5%
1.10
1.56
0.003
No bicycle
3416
48.2%
279
40.8%
3695
47.5%
Ref
Motorcycle or
scooter
Motorcycle or
scooter
owned No
2279
32.1%
240
35.1%
2519
32.4%
0.94
1.34
0.194
motorcycle or
scooter
4814
67.9%
443
64.9%
5257
67.6%
Ref
Car or truck
Car or truck
owned
No car/truck
owned
178
6915
2.5%
97.5%
13
670
1.9%
98.1%
191
7585
2.5%
97.5%
0.47
Ref
1.53
0.586
Wealth
ranking
Nonpoor
households
3525
49.7%
309
45.2%
3834
49.3%
0.85
1.38
0.513
Poorest 40% of
households
3568
50.3%
374
54.8%
3942
50.7%
Ref
Mother’s Characteristics and Household Socio-Economic Factors
Significantly higher proportions of children dying are found in the following groups:

116
● Among mothers with no education (72.0%) versus (28.0%) for those with
education.
● Among mothers who are working (77.5%) versus (22.5%) not working.
● Among younger mothers below 29 (53.9%) versus older mothers (46.1%).
● Those who were not weighed (47.9%) , as compared with those from written
cards (16.7%); and those from mother`s recall (23.0%).
● During the neonatal period, there is a higher under -five mortality rate
respectively for 0–28 days/neonatal (43.2%) , 1-11 months/post-neonatal (40.7%)
, and 12–59 months/child (16.1%). After assessing the relationship between
mother’s characteristics and under 5 Mortality/Survival, the following
characteristics were statistically significantly associated with child survival
(Table 12) mother working, mother over 29 years old, and child with either a
documented weight at birth or mother who could recall the childbirth weight.
Table 12.

117
Household Socio-economic Factors and Mother’s Characteristics and Under-five Survival
Results
A total of 7,776 children under 5 years old were examined from the surveyed
women (15-49 years old) drawn from the merged 2005-2020 DHS datasets of Cote
D’Ivoire. The majority (53.6%) of them were 12-59 months old child, followed by the 0-
28 days (24.6%) neonatal, and 1-11 months/post-neonatal (21.8%).The vast majority
(83%) had a birth card, and 70.8% received mother breast milk for at least six months.
Most (58.2%) of the mothers enrolled were young and less than 30 years old. More than
Child Status
Characteristics
Child Alive
Child Died
Total
95.0% CI
pvalue
N
%
n
%
N
%
Lower
Upper
Mother education
status
Some education
No education
2,324
4,769
32.8%
67.2%
191
492
28.0%
72.0%
2,515
5,261
32.3%
67.7%
0.73
Ref
1.10
Ref
0.295
Mother
employment status
Working
Not working
5,036
2,057
71.0%
29.0%
529
154
77.5%
22.5%
5,565
2,211
71.6%
28.4%
1.20
Ref
1.80
0
Husband/partner
education status
Some education
No education
2,472
4,398
36.0%
64.0%
214
444
32.5%
67.5%
2,686
4,842
35.7%
64.3%
0.79
REf
1.17
0.678
Mother husband or
partner status
With a partner
Without a partner
6,058
1,035
85.4%
14.6%
590
93
86.4%
13.6%
6,648
1,128
85.5%
14.5%
0.73
Ref
1.24
0.718
Mother age
Older mother > 29
years
Young mother ≤29
years
2,932
4,161
41.3%
58.7%
315
368
46.1%
53.9%
3,247
4,529
41.8%
58.2%
1.28
Ref
1.82
0
Weight at
birth/recall
Not weighted
From written card
From mother`s recall
2,635
2,942
1,234
37.1%
41.5%
17.4%
327
114
157
47.9%
16.7%
23.0%
2,962
3,056
1,391
38.1%
39.3%
17.9%
Ref
0.23
1.03
0.36
1.61
0
0.03
Don`t know
30
0.4%
13
1.9%
43
0.6%
1.85
8.03
0
Special answers
252
3.6%
72
10.5%
324
4.2%
2.54
4.91
0

118
half (67.7%) of the mothers didn’t have a formal education and the majority of them
(85.5) were living with a male partner.
Among them, 49.5% (3852) were female and 5.5% (3924) males (Table 8). Of
the sample observed, a total of 683 (8.8%) deaths were reported (Table 10) of which
(43.2%) occurred between birth and 28 days (neonatal mortality), (40.7%) occurred
between one (1) to 11 months (postnatal mortality), and (16.1%) occurred between 12 to
59 months (child mortality) (Table 10). Based on gender of the children died ,more than
half of the children (61.6%) were male whilst 38.4% were female (Table 10).There is a
higher proportion of deaths occurring in households with 1 or 0 children cared for
respectively 47.3% for more than 2 children versus 52.7% for 1 or 0) (Table 10). Also,
significantly lower proportions of children dying in Centre-Nord, Centre-Ouest and
Sudouest.
Based on an analysis of the confounding factors in this study, most of the women
and children under-five came from a rural (71.2%) versus urban (28.8%) setting (Table
10). Based on the household wealth, Richer households (45.2%) have a lower rate of
mortality versus Poorest households (54.8%) (Table 12). Male headed households have a
higher under 5 mortality (86.2%) versus women Female headed households (13.8%)
(Table 11). Furthermore, looking at education, the results show that a higher rate of
under- five mortality are among mothers with no education (72.0%) versus (28.0%) for
those with education (Tables 10 &12).

119
Multivariate Analysis (Cox Regression)
I fitted Cox proportional regression model to the data with the factors (WaSH) and
confounding variables which included demographic, socioeconomic, and maternal
variables to check the magnitude of their effect on the outcome variable (death of child or
U5M). One considerable limitation of the model is associated with its own assumptions,
including the proportionality assumption. This assumption assumes that the hazard ratio
is constant over time, and this also could represent a limitation; therefore, care must be
taken to test this assumption (Bewick et al., 2004). The proportionality assumption of the
cox proportional regression method must be assessed. In fact, the model presumes that
the ratio of the hazard functions for any two subgroups (i.e., two groups with different
values of the explanatory variable X) is constant over time (Dickman, 2005). So, if the
hazard functions cross, there is a possibility that the effect of the independent variable
will not be statistically significant despite the presence of a clinically interesting effect.
Therefore, it is essential to plot survival curves before fitting Cox proportional models.
Among several methods to test this assumption, include a) Plot the cumulative survivor
functions and check if they do not cross, b) Plot the log cumulative hazard functions over
time and check if they are parallel, c) Include time-by-covariate interaction terms in the
model and test statistical significance, d) Plot Schoenfeld’s residuals against time to
identify patterns (Dickman, 2005).
Testing Cox Regression Assumption
As mentioned in the earlier section, the proportional hazard assumption is that the
hazard function or hazard ratios for censored and uncensored groups are proportional

120
over time, which means that the hazard ratio is constant over time. I tested the
assumption prior to undertaking the full analysis through Cox regression model. I used
the following approach to test the assumption:
● Visual examination of the Kaplan–Meier curves to check if there is a crossing of
the Kaplan–Meier curves which indicate a violation of the assumption; or if rates
of change of the two curves were not constant over time.
● Fitting a Cox regression model with the relevant factor, and testing for interaction
with the time variable. In SPSS, the factor of interest (water, sanitation, hygiene),
and the product of the time variable with the same factor (T_COV_) were added
to the model. If a significant model can be developed (p <0.05), then the
proportional hazards assumption is not valid. If p>0.05, then the proportionality
assumption is valid. The results from the three factors of interest are given below.
Tests of Model Fit for Sanitation as the Factor or Explanatory Variable
● Cox regression model was fitted with relevant factors (sanitation) to test for
interaction with time variables using SPSS, and the product of the time variable
with the same factor (T_COV_) was added to the model. If a significant model
can be developed with (p <0.05), this indicates that the proportional hazards
assumption is not valid. Fortunately, in the present case p>0.05, as seen in Table
13 (Sig= 0.484).By fitting a Cox regression model with the relevant factor
(sanitation), and a test for interaction with time variable (T_COV_) did not produce
121
significant interactions. This means that the fitted model did not have time-dependent
hazards. Which means that the proportionality assumption is met. Table 13
Testing of interaction with sanitation and time variable using SPSS to diagnose the
Cox proportionality assumption
Variables in the Equation
B
SE
Wald
Df
Sig.
Exp(B)
T_COV_
0.005
0.009
0.295
1
0.587
1.005
Sanitation facility type
0.067
0.096
0.489
1
0.484
1.07
Proportional hazard assumption is valid (p>0.05) for the interaction.
Furthermore, as Figure 5 shows, the graphical plotting using Kaplan–Meier
curves indicates two parallel curves which do not cross, and this implies that there is no
violation of the assumption; or because the rates of change of the two curves were
constant over time. In sum, fitting a Cox regression model with the relevant factor
(sanitation), and testing for interaction with the time variable (T_COV_) did not produce
significant interactions. Moreover, the curves were parallel as expected for a valid
proportional hazard context. This means that the fitted model did not have significant
time-dependent hazards. I concluded that the fitted model shows that the proportionality
assumption for Cox regression is met.
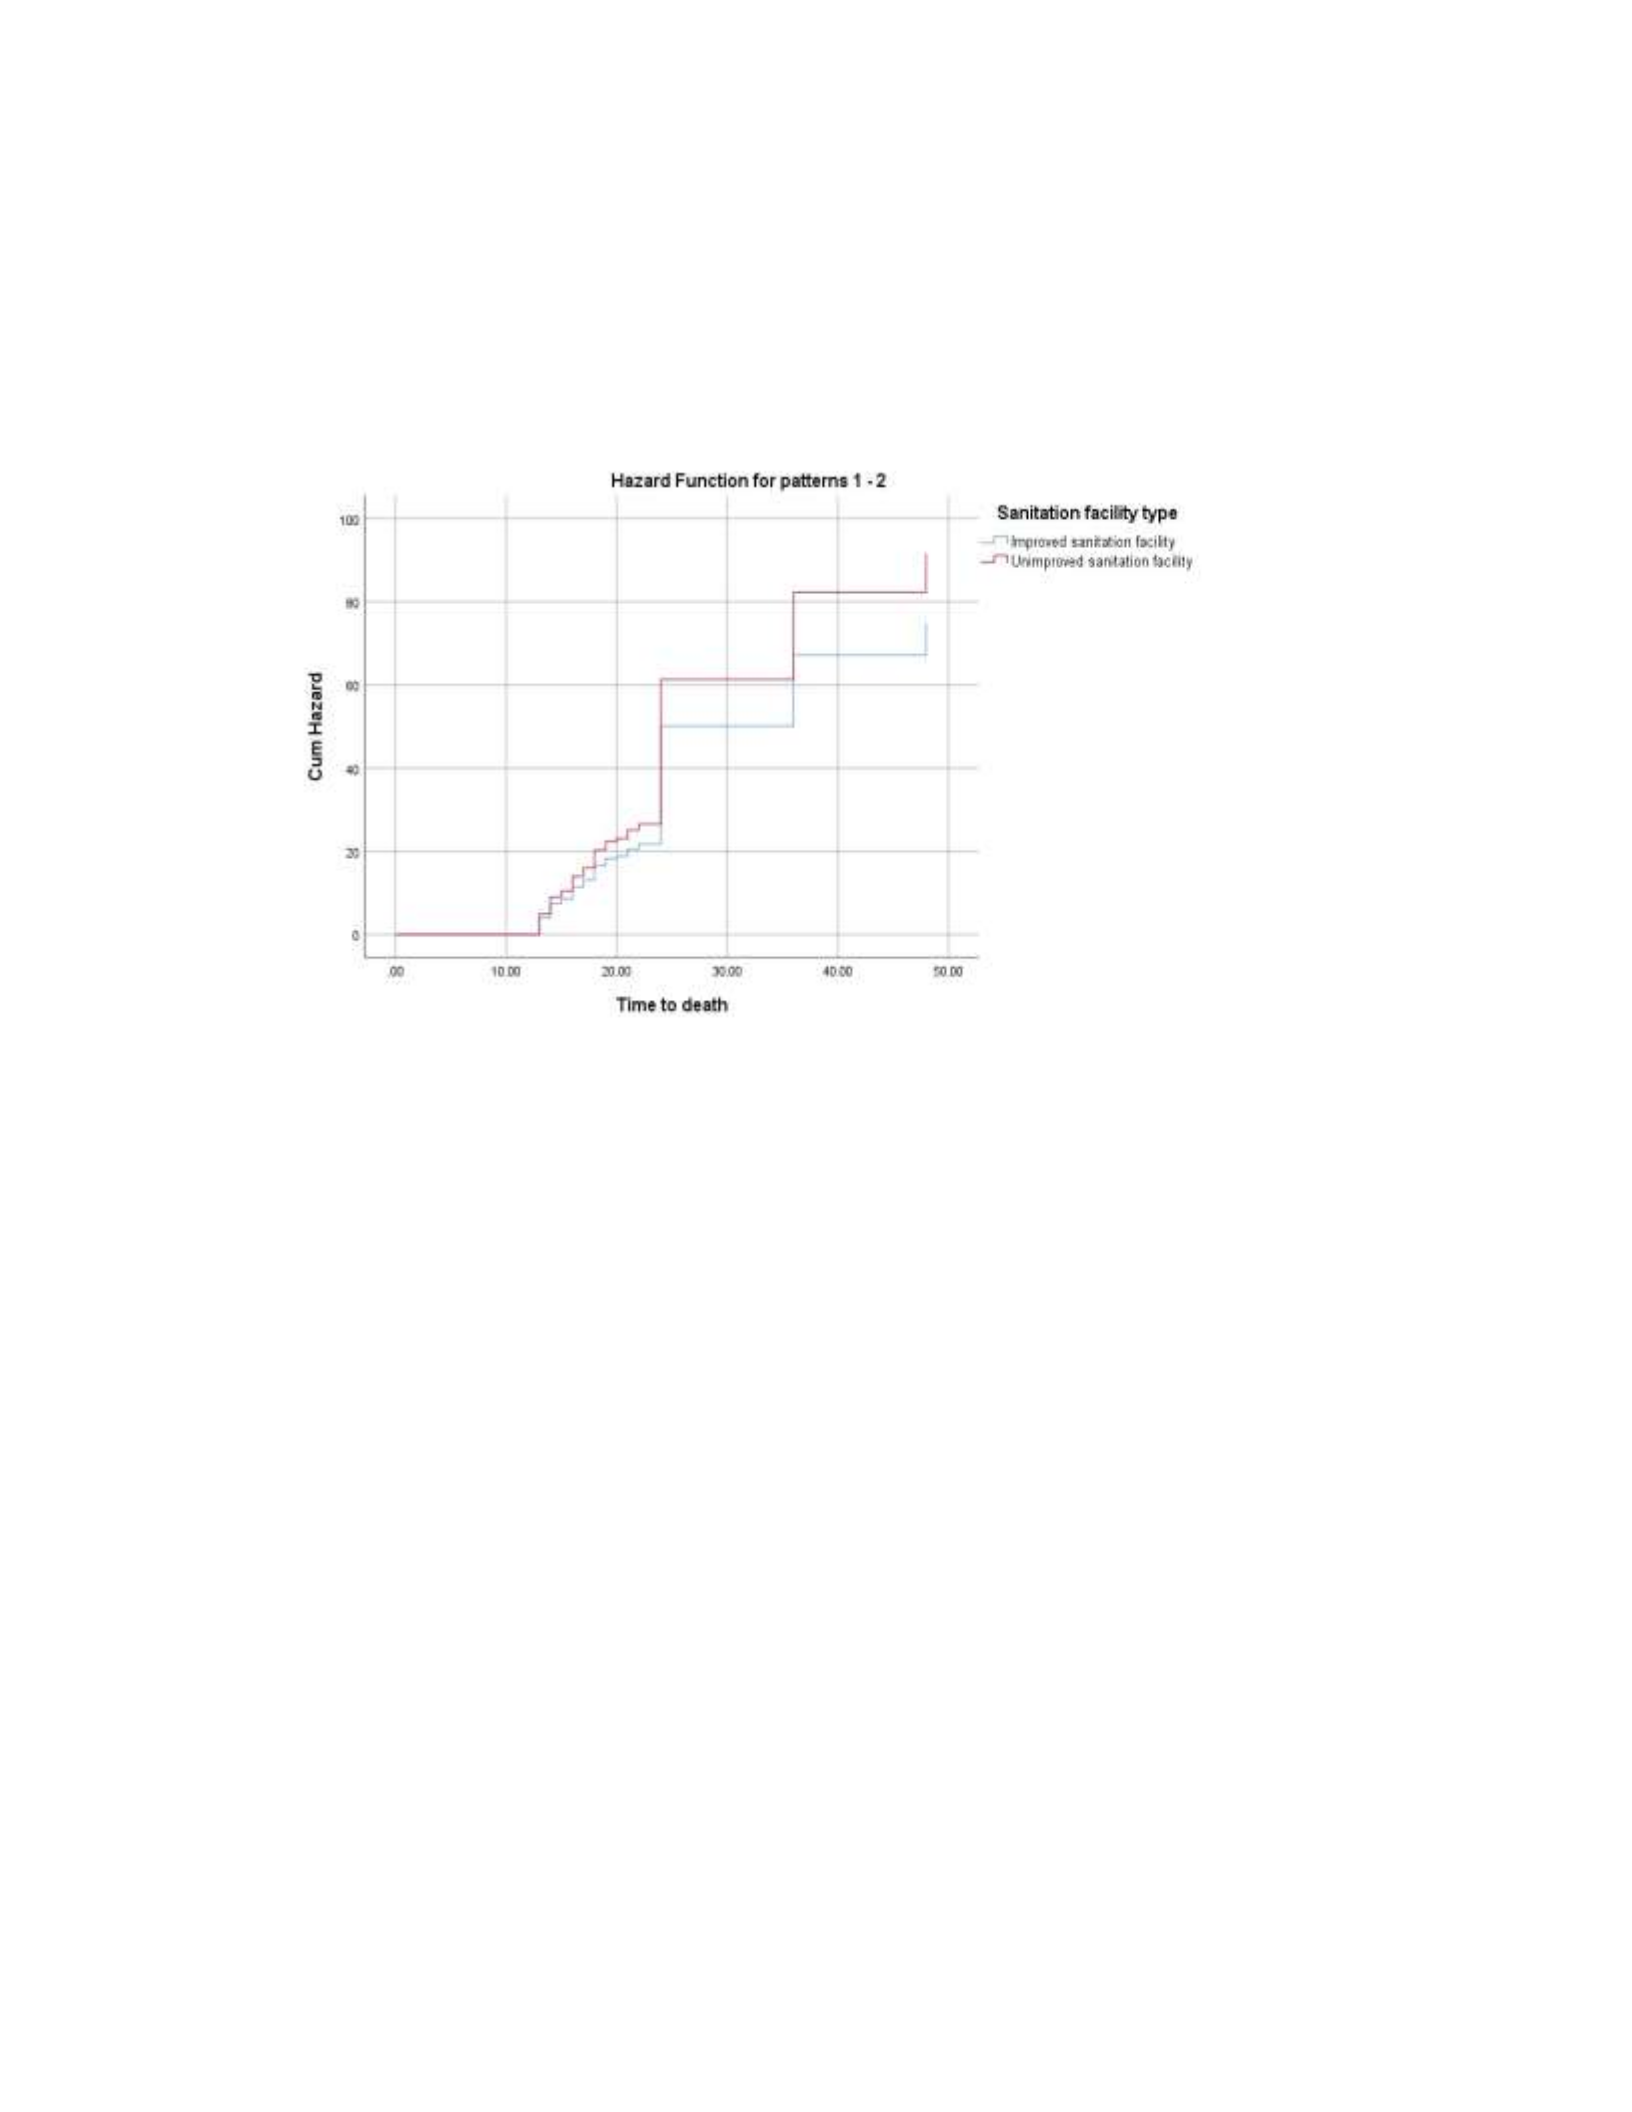
122
Figure
5.
Testing assumption for Hazard function by type of Sanitation facility (Patterns 1-2)
Tests of Model Fit: Water as the Independent Variable
For this model, tests show model assumptions holding: (1) survival curves for
different strata must have hazard functions that are proportional over the time and (2) the
relationship between the log hazard and each covariate is linear. Fitting a Cox regression
model with the relevant factor (water), and testing for interaction with the time variable
(T_COV_) did not produce significant interactions. This means that the fitted model did
not have significant time-dependent hazards.
● Cox regression model was fitted with a relevant factor (water) to test for
interaction with the time variable using SPSS, and the product of the time variable
with the same factor (T_COV_) was added to the model. If a significant model
123
can be developed with (p <0.05), this indicates that the proportional hazards
assumption is not valid. Fortunately, in the present case p>0.05, as seen in Table
14 (Sig=.892) .By fitting a Cox regression model with the relevant factor (water),
and testing for interaction with time variable (T_COV_) did not produce
significant interactions. This means that the fitted model did not have
timedependent hazards and the proportionality assumption is met.
Table 14.
Testing of interaction with Water and time variable using SPSS to diagnose the Cox
proportionality assumption
B
SE
Wald
Df
Sig.
Exp(B)
T_COV_
0.001
0.009
0.014
1
0.906
1.001
Water source
0.015
0.109
0.018
1
0.892
1.015
Proportional hazard assumption is valid (p>0.05) for the interaction.
Furthermore, as Figure 6 shows, the graphical plotting using Kaplan–Meier
curves indicates two parallel curves which do not cross, and this implies that there is no
violation of the assumption; or because the rates of change of the two curves were
constant over time. In sum, fitting a Cox regression model with the relevant factor
(sanitation), and testing for interaction with the time variable (T_COV_) did not produce
significant interactions. Moreover, the curves were parallel as expected for a valid
proportional hazard context. This infer that the fitted model did not have significant
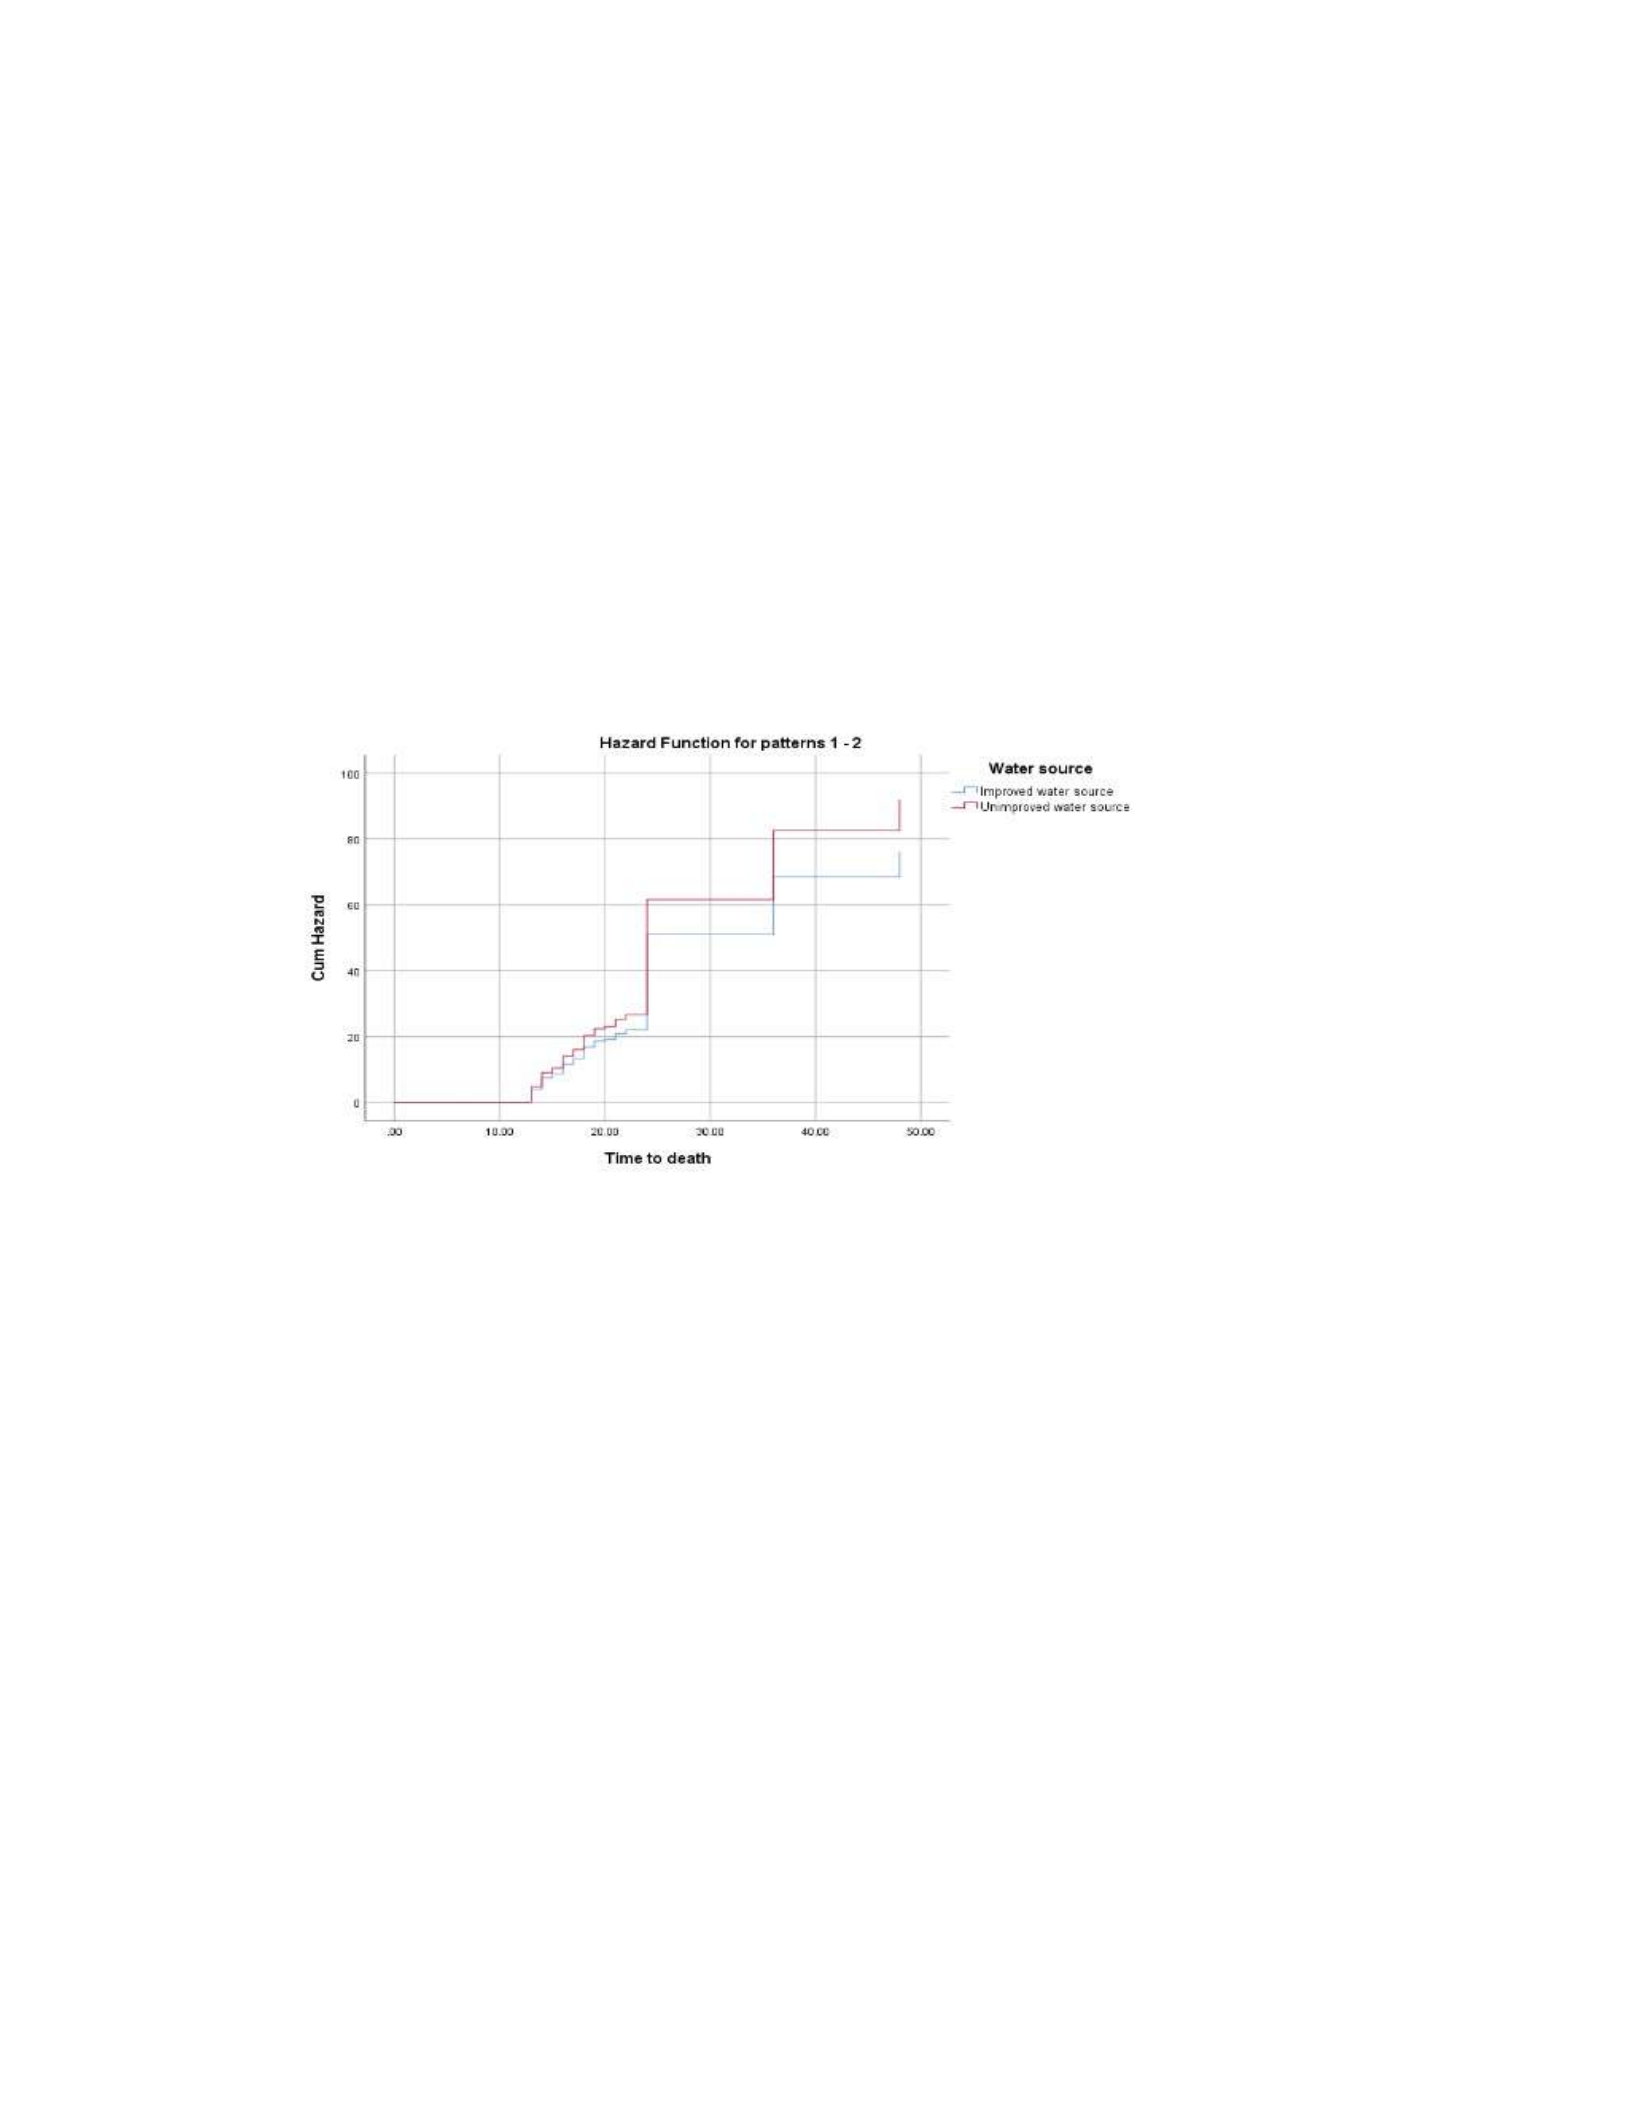
124
Figure
timedependent hazards. I concluded that the fitted model shows that the proportionality
assumption for Cox regression is met.
. 6
Testing assumption. Testing assumption for Hazard function by type of Water source
(Patterns 1-2)
Tests of Model Fit: Hygiene the Independent Variable
For this model, tests show model assumptions holding: (1) survival curves for
different strata must have hazard functions that are proportional over the time and (2) the
relationship between the log hazard and each covariate is linear.
● Cox regression model was fitted with relevant factor (hygiene) to test for
interaction with time variable using SPSS, and the product of the time variable
with the same factor (T_COV_) was added to the model. If a significant model
can be developed with (p <0.05), this indicates that the proportional hazards
assumption is not valid. Fortunately, in the present case p>0.05, as seen in Table

125
15 ( Sig=.410) . By fitting a Cox regression model with the relevant
factor
(hygiene), and testing for interaction with time variables (T_COV_) did
not
produce significant interactions. This means that the fitted model did not have
time-dependent hazards, implying that the proportionality assumption is met.
Table 15.
Testing of interaction with hygiene and time variable using SPSS to diagnose the Cox
proportionality assumption
B
SE
Wald
Df
Sig.
Exp(B)
T_COV_
0.005
0.015
0.124
1
0.724
1.005
Hygiene adequacy 0.142 0.173 0.678 1 0.41 1.153
In addition, as figures 7 indicates, the graphical plotting using Kaplan–Meier
curves indicate two parallel curves which do not cross, and this implies that there is no
violation of the assumption; or because the rates of change of the two curves were
constant over time. In sum, fitting a Cox regression model with the relevant factor
(sanitation), and testing for interaction with the time variable (T_COV_) did not produce
significant interactions. Moreover, the curves were parallel as expected for a valid
proportional hazard context. This infers that the fitted model did not have significant
time-dependent hazards. I concluded that the fitted model shows that the proportionality
assumption for Cox regression is met.
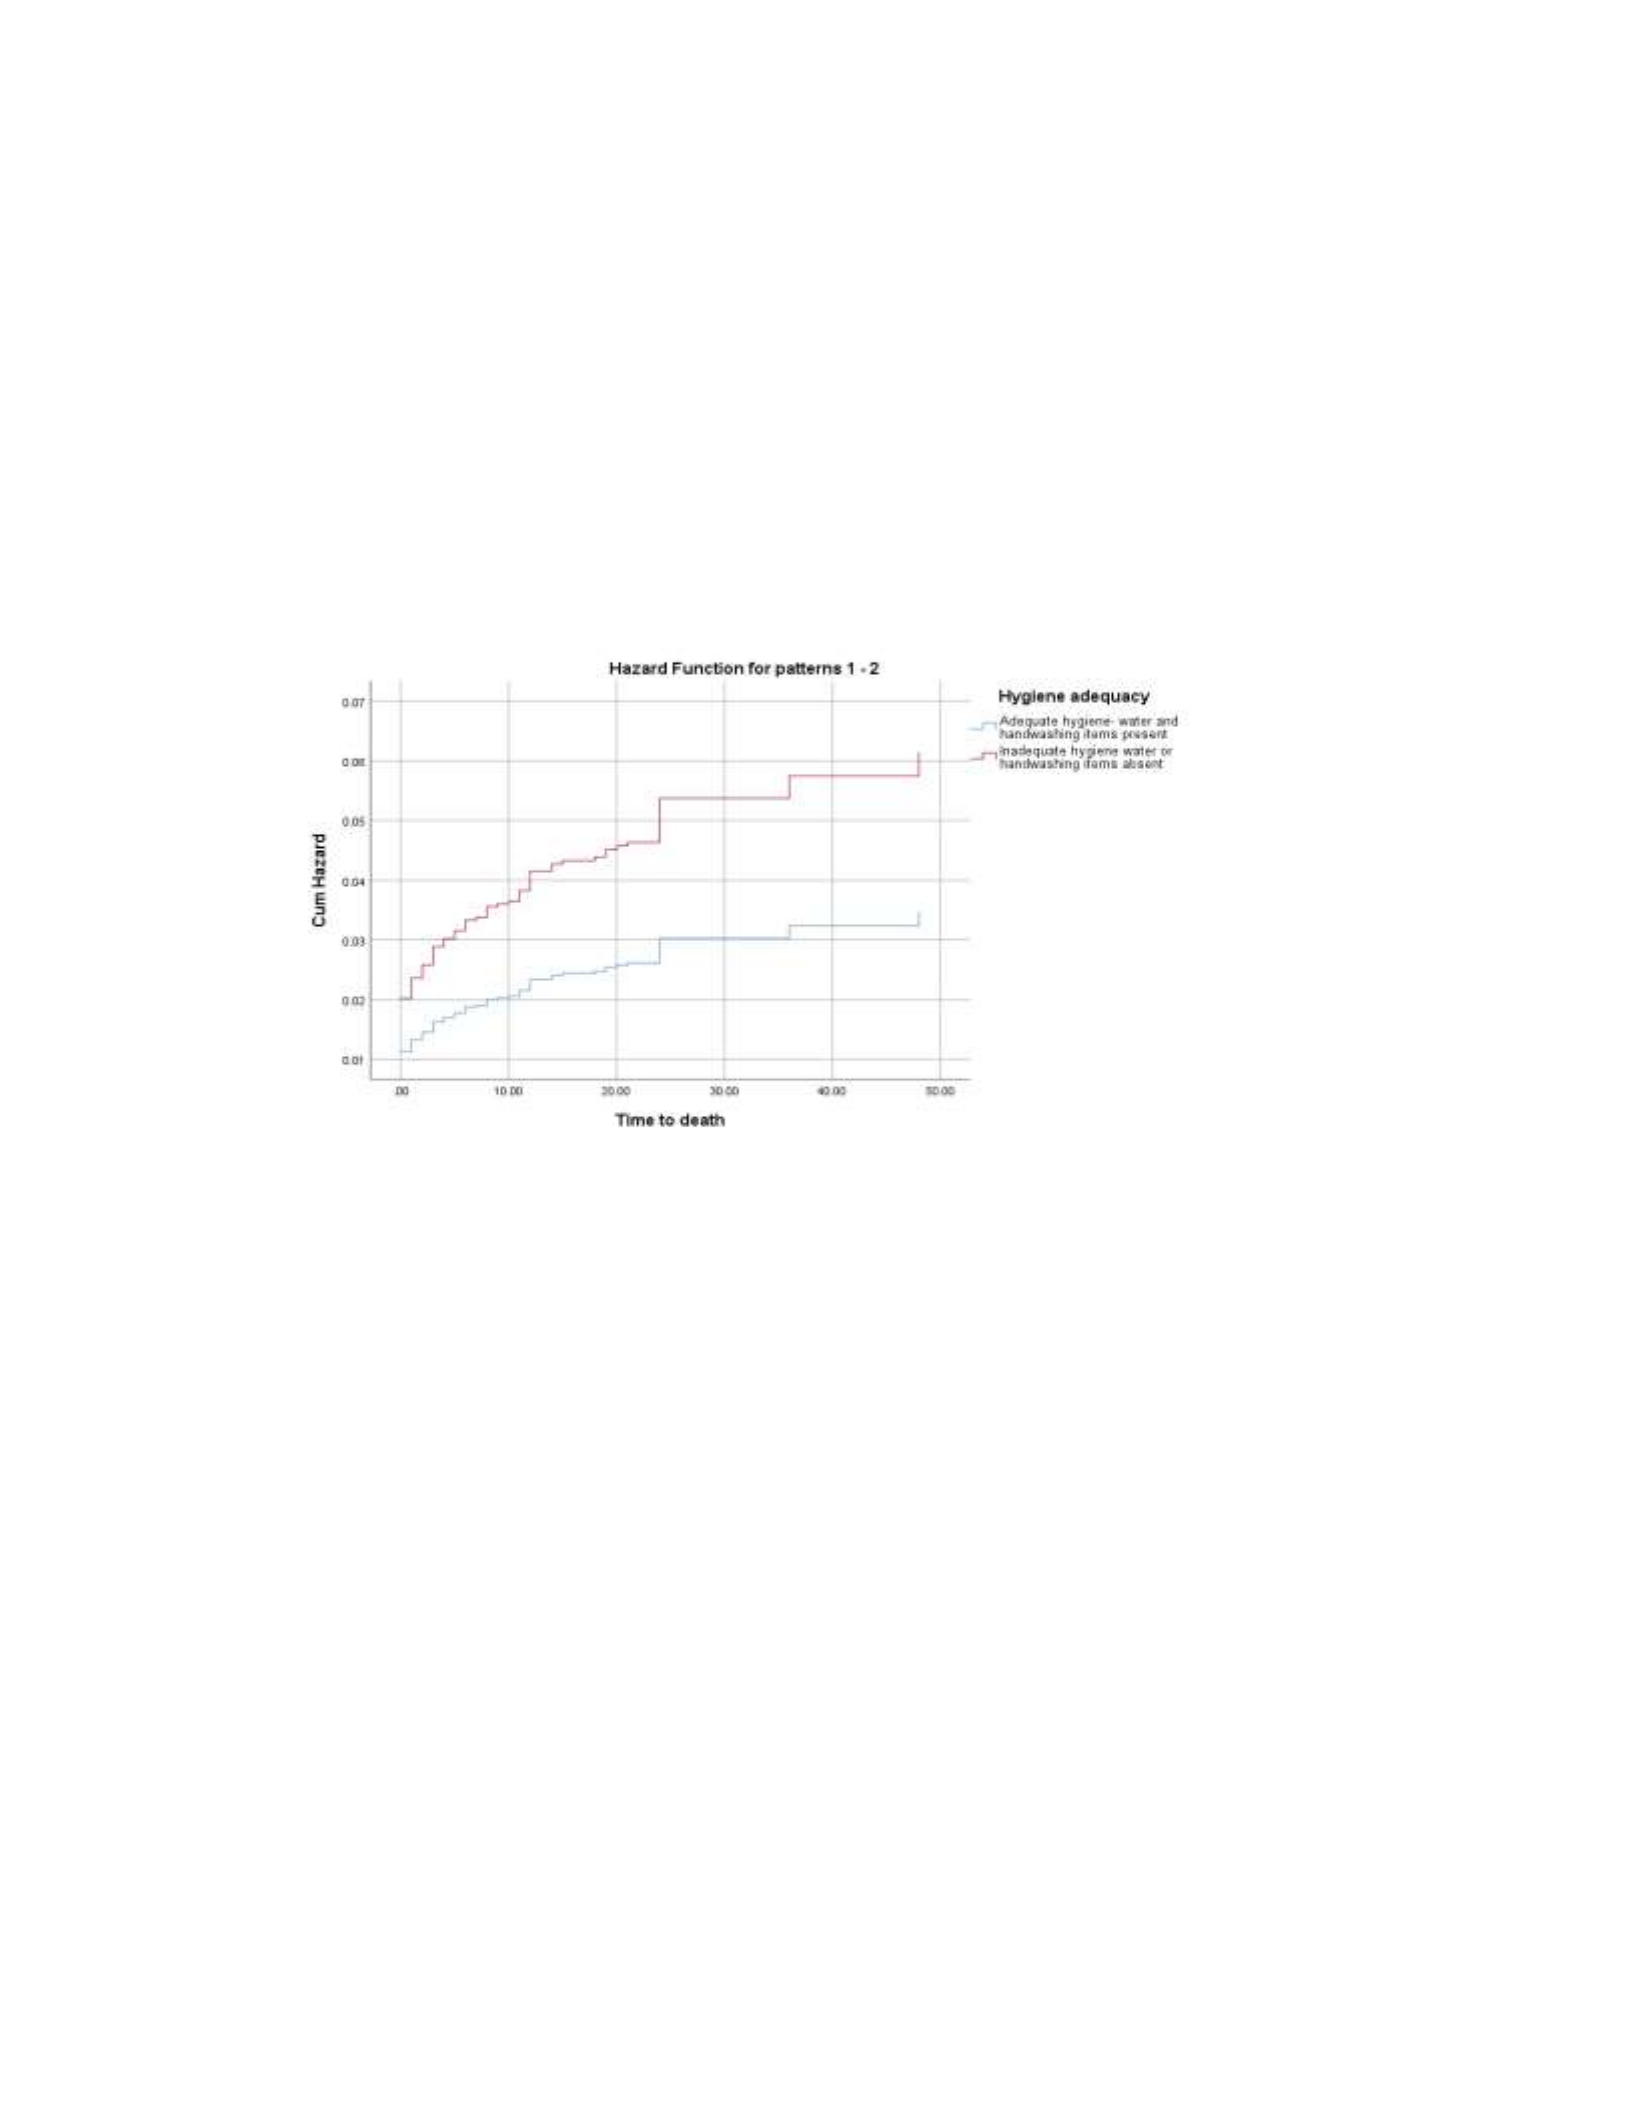
126
Figure
7
Testing assumption. Testing assumption for Hazard function by hygiene adequacy
(Patterns 1-2)
Tests of Model Fit: WaSH
The baseline hazard is proportional if the graphs are parallel to each over;
therefore, do not cross. Given the elements cited above, these curves are parallel (Figure
8) ; hence do not cross. Assuming that my visual observation is accurate, so I concluded
that the assumption of proportionality is appropriate; hence, has been met. However, as
Xue et al. (2013) suggested “graphical methods involve a moderate degree of subjectivity
in interpretation” (p. 2). Given the facts described above, I concluded that the
assumption of proportionality is met; therefore, my planned methodology will not be
affected by a potential non-proportionality element in dealing with the present research
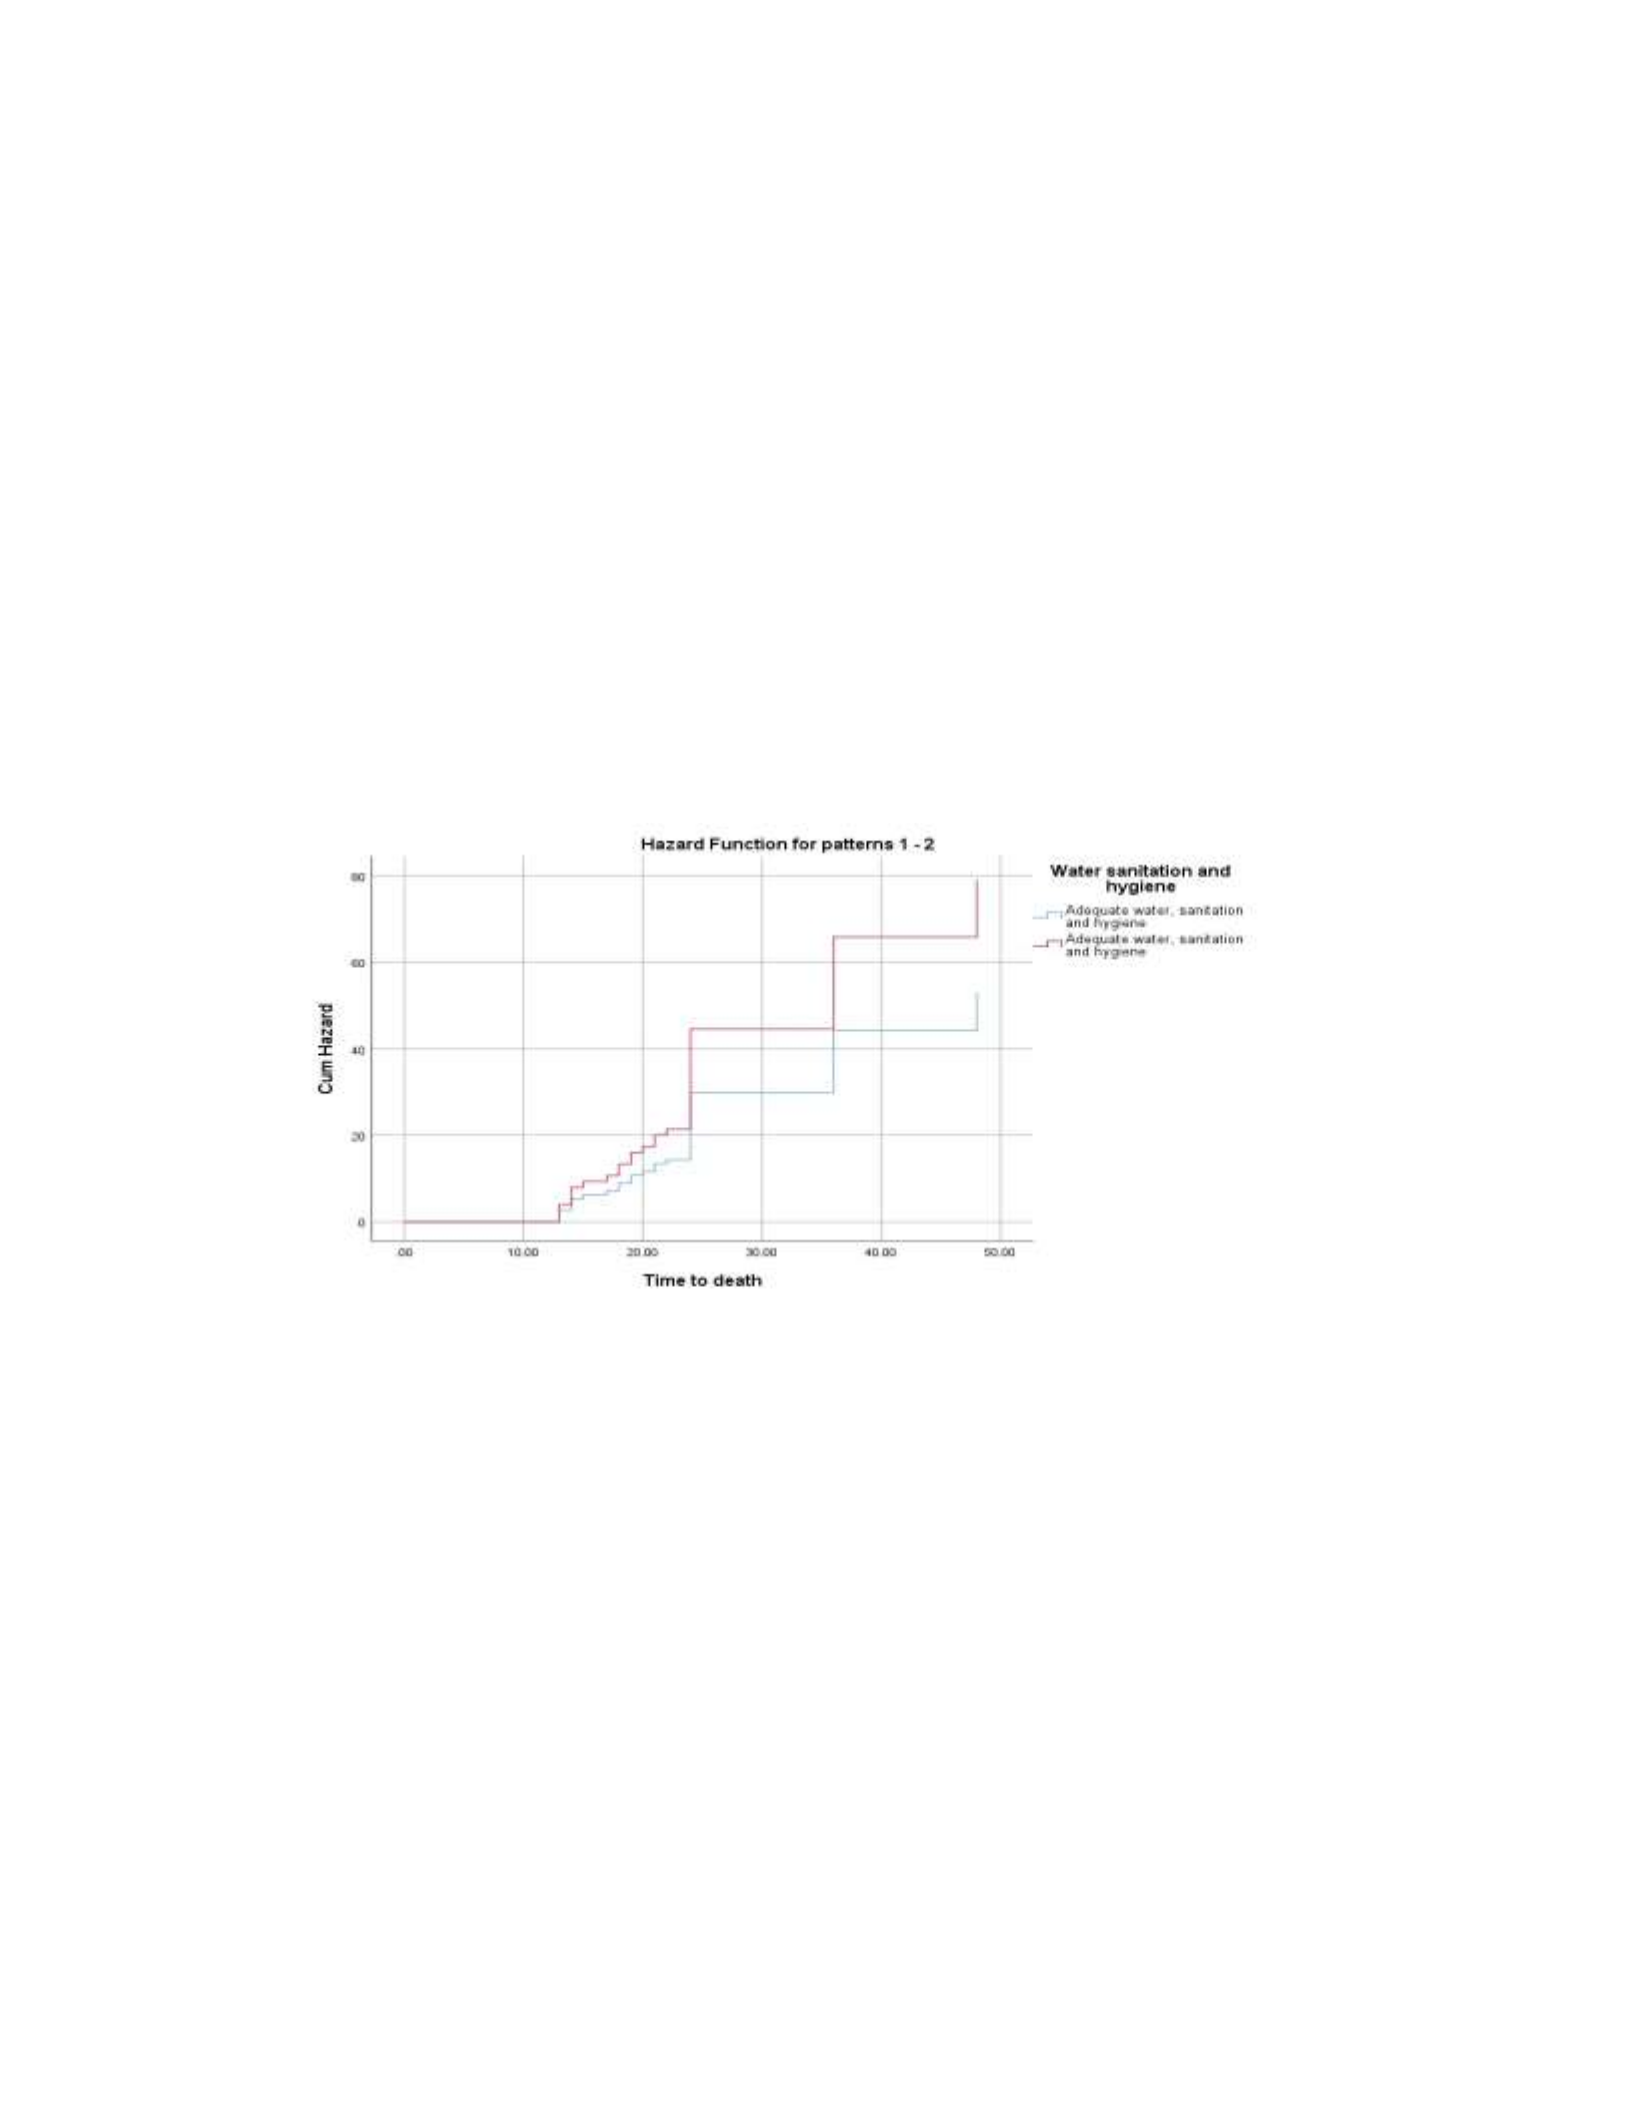
127
design and method. Graphical approaches are a visual form of screening for
nonproportionality which can provide insight into the temporality and the extent of
nonproportionality that is otherwise difficult to obtain using statistical methods (Xue et
al.,
2013, p.2).
Figure 8
Testing assumption: WaSH variables
Research Question1(RQ1):To what extent does access to improved sanitation
facilities affect the under-five mortality among women 15-49 in Cote D’Ivoire while
controlling for demographic, socioeconomic , and maternal variables
The null hypothesis (H01):There is no statistically significant difference in the
under 5 mortality while controlling for demographic ,socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
sanitation facilities and those without.

128
Figure
The alternative hypothesis (HA1):There is statistically significant difference in the
under 5 mortality while controlling for the demographic ,socioeconomic, and

129
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
sanitation facilities and those without
For Research Question 1, I conducted Cox proportional regression analysis to examine
the effect of access sanitation facilities on the under 5 mortality among women 15-49
while controlling for demographic, socioeconomic, and maternal variables. The results
show that there is a statistically significant difference in the under-five mortality
associated with access to sanitation facilities (p=0.013). It implies that children from
households using unimproved sanitation facilities have a higher risk of death 1.224
times more (HR: 1.224, 95% CI: 1.044- 1.435) as compared to those coming from
households with improved sanitation facilities (Table 17).
Based on the results, there is a statistically significant relationship between the
under-five mortality and access to improved sanitation sources (Sig=0.013 <0.05) (Table
17); I therefore reject the null hypothesis in favor of the alternative. I concluded that
women with unimproved access to sanitation facilities have (22%) risk of under-five
mortality compared to counterparts with improved sanitation facilities.
Beside the hazard ratio in the model, the chi square (χ2) test often tests for
evidence of any difference in the survival functions across all strata for categorical
variables or for a unit increase for continuous variables (Wilson, 2018). The model is
valid if the omnibus tests of model coefficients are significant (that is, p < 0.05). Thus,
the fitted model suggested that the coefficients of the model are non-zero (χ2=1785.982,
P=000<0.05) suggesting that the model best fit the data. The p-value or Sig = 000 less

130
than 0.05 (Table 16) indicates sufficient evidence of a clear association between the risk
of death and the study of independent variables and confounders included in the model.
In sum, the results from the omnibus test showed the model is statistically significant, p =
000 < alpha = .05, thus the model adequately predicts the effect of the independent
variables on under 5 mortality (See Tables 16).
Table 16.
Omnibus Tests of Model Coefficients
Change From Previous Change From Previous
Overall (score)
-2 Log Step Block
Likelihood
Chisquare
Df
Sig.
Chisquare
Df
Sig.
Chisquare
df
Sig.
10096.389
1552.1
7
10
0
1785.9
8
9
0
1785.9
8
9
0
Table 17.
Variables in the Equation
Variables B
Variables in the Equation
SE
95.0% CI
Wald Df Sig. Exp(B)
Lower Upper
Sanitation facility type 0.20 0.081 6.233 1 0.013 1.224 1.04 1.44
Under-five mortality age
1.531 2 0.465
group
Under-five mortality 1.4E+1
-11.42 17.753 0.414 1 0.52 0 0.00
age group (1) 0
Under-five mortality 5.9E+0

131
-22.82 20.771 1.207 1 0.272 0 0.00
age group (2) 7
Mother education status 0.32 0.087 13.573 1 0 1.378 1.16 1.63
Mother employment
status
-0.36
0.093
14.923
1
0
0.698
0.58
0.84
Mother age
-0.31
0.08
15.352
1
0
0.731
0.63
0.86
Weight at birth/recall
0.21
0.037
32.689
1
0
1.233
1.15
1.32
Household size
-0.17
0.118
1.987
1
0.159
0.846
0.67
1.07
Gender of child
Number of under 5 cared
-0.41
0.079
26.874
1
0
0.664
0.57
0.78
for
0.84
0.084
99.014
1
0
2.317
1.96
2.73
Water
Research Question 2 (RQ2):To what extent access to improved water sources affect the
under 5 mortality among women 15-49 in Cote D’Ivoire while controlling for
demographic, socioeconomic ,and maternal variables ?
The null hypothesis (H02):There is no statistically significant difference in the
under 5 mortality while controlling for the demographic ,socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
water sources and those without.
The alternative hypothesis (HA2) :There is a statistically significant difference in
the under 5 mortality while controlling for the demographic ,socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
water sources and those without .

132
For Research Question 2, I conducted cox proportional regression analysis to examine the
effect of access to improved water sources on the under 5 mortalities among women 1549
while controlling for demographic, socioeconomic, and maternal variables. The results
indicate that there is a statistically significant difference in the under-five mortality
associated with access to improved water sources (p=0.050). Based on the level of hazard
from the inferential analysis, women from households using unimproved water sources
have a higher risk of U5M 1.205 time more (HR: 1.205, 95% CI: 1.000- 1.453) (p=0.050)
as compared to those coming from households with improved water sources (Table 19).
Looking at both the confidence interval and the P value, this result appears statistically
significant (Sig=0.050 < or equal 0.05) and CI: (1.000- 1.453). I, therefore, rejected the
null hypothesis in favor of the alternative. I concluded that women with access to
unimproved water sources have (20%) risk of under 5 mortality compared to counterparts
with improved water sources. The fitted model was significant (with Sig less than 0.05);
therefore the method is justified and valid (Table 18).
Table 18.
Omnibus Tests of Model Coefficients
-2 Log
Likelihood
Overall (score)
Change From Previous Step
Change From Previous
Block
Chi-
Df
square
Sig.
Chi-
Df Sig.
square
Chisquare
df
Sig.
10014.503
1664.297 20
0
1615.8
6 0
1
1615.8
1
6
0
a. Beginning Block Number 3. Method = Enter
Table 19.
Variables in the Equation

133
Variables
Variables in the Equation
B
SE
Wald
Df
Sig.
Exp(B
)
95.0
Lowe r
% CI
Upper
Water source
0.19
0.10
3.84
1
0.05
1.21
1.00
1.45
Gender of child
-0.37
0.08
22.17
1
0.00
0.69
0.59
0.81
Number of under 5 cared for
0.94
0.08
142.8
5
1
0.00
2.56
2.19
2.98
Place of residence
0.25
0.10
6.14
1
0.01
1.28
1.05
1.57
Region
91.20
10
0.00
Region (1)
-0.17
0.19
0.78
1
0.38
0.85
0.58
1.23
Region (2)
-0.38
0.21
3.17
1
0.08
0.69
0.45
1.04
Region (3)
-0.61
0.22
7.96
1
0.01
0.54
0.35
0.83
Region (4)
0.48
0.16
8.44
1
0.00
1.61
1.17
2.22
Region (5)
0.01
0.19
0.00
1
0.98
1.01
0.70
1.45
Region (6)
0.58
0.16
13.62
1
0.00
1.78
1.31
2.41
Region (7)
-0.02
0.19
0.01
1
0.92
0.98
0.68
1.41
Region (8)
-0.31
0.21
2.12
1
0.15
0.74
0.49
1.11
Region (9)
-0.46
0.22
4.57
1
0.03
0.63
0.41
0.96
Region (10)
-0.02
0.21
0.01
1
0.92
0.98
0.65
1.47
Under-five mortality age
group
1.53
2
0.47
Under-five mortality age
group (1)
-
11.4
4
17.8
6
0.41
1
0.52
0.00
0.00
1710980
7
Under-five mortality age
group (2)
-
22.8
3
20.8
6
1.20
1
0.27
0.00
0.00
6998259
6
Mother education status
0.17
0.09
3.71
1
0.05
1.19
1.00
1.42
Mother employment
status
-0.37
0.09
15.83
1
0.00
0.69
0.57
0.83
Mother age
-0.26
0.08
10.58
1
0.00
0.78
0.67
0.90
Weight at birth/recall
0.25
0.04
48.46
1
0.00
1.29
1.20
1.39

134
Hygiene
Research Question 3(RQ3): To what extent does adequate hygiene affect the under 5
mortalities among women 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables?
The null hypothesis (H03): There is no statistically significant difference in the
under-five mortality while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with adequate hygiene
and those without.
The alternative hypothesis (HA3): There is a statistically significant difference in
the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with adequate hygiene
and those without
For Research Question 3, I conducted cox proportional regression analysis to
examine the effect of adequate hygiene on the under 5 mortalities among women 15-49
while controlling for demographic, socioeconomic, and maternal variables. The results
indicate that there is a statistically significant difference in the under 5 mortality
associated with adequate hygiene (p=0.013). It implies that women from households
using inadequate hygiene have a higher risk of under 5 deaths 1.773 times more (HR:
1.773 ,95% CI: 1.129- 2.784) (p=0.013) as compared to those coming from households
with adequate hygiene (Table21).

135
Based on the results, there is a statistically significant relationship between the
under-five mortality and adequate hygiene (Sig= P=0.013<0.05); I therefore, rejected the
null hypothesis in favor of the alternative. I concluded that women with access to
inadequate hygiene have (77%) risk of under 5 mortality compared to counterparts with
adequate hygiene. The fitted model was significant (with Sig less than 0.05); therefore the
method is justified and valid (Table 20).
Table 20.
Omnibus Tests of Model Coefficients
Change From Previous Change From Previous
Overall (score)
-2 Log Step Block
Likelihood
Chisquare
Df
Sig.
Chisquare
Df
Sig.
Chisquare
Df
Sig.
1864.896
115.96
9
19
0
16.957
1
0
16.957
1
0
a. Beginning Block Number 3. Method = Enter Table
21.
Variables I n the Equation
Variables B
Variables in the Equation
SE Wald Df
Sig.
Exp(B)
95.0% CI
Lower Upper
Hygiene adequacy
0.57
0.23
6.18
1
0.01
1.77
1.13
2.78
Mother education status
-0.09
0.18
0.25
1
0.62
0.91
0.64
1.30
Mother employment
status
0.02
0.20
0.01
1
0.93
1.02
0.69
1.50
Mother age
-0.26
0.18
2.08
1
0.15
0.77
0.54
1.10
Weight at birth/recall
1.27
0.19
45.09
1
0.00
3.54
2.45
5.13
136
Household size
0.17
0.28
0.40
1
0.53
1.19
0.69
2.05
Gender of child
-0.52
0.18
8.21
1
0.00
0.59
0.42
0.85
Number of <5 cared
for
0.88
0.19
20.46
1
0.00
2.40
1.64
3.51
Region
14.55
10
0.15
Region (1)
0.85
0.47
3.31
1
0.07
2.35
0.94
5.88
Region (2)
0.17
0.50
0.12
1
0.73
1.19
0.45
3.13
Region (3)
-0.08
0.49
0.03
1
0.87
0.92
0.35
2.42
Region (4)
0.66
0.48
1.90
1
0.17
1.93
0.76
4.94
Region (5)
0.58
0.44
1.71
1
0.19
1.79
0.75
4.26
Region (6)
1.07
0.44
5.86
1
0.02
2.92
1.23
6.96
Region (7)
0.08
0.45
0.04
1
0.85
1.09
0.45
2.63
Region (8)
0.50
0.43
1.38
1
0.24
1.65
0.72
3.79
Region (9)
0.08
0.51
0.02
1
0.88
1.08
0.40
2.95
Region (10)
Birth weight in
0.52
0.39
1.74
1
0.19
1.68
0.78
3.64
kilograms (2
decimals)
-0.46
0.12
16.07
1
0.00
0.63
0.50
0.79
Water, Sanitation, and Hygiene Combined
Research Question 4 (RQ4): To what extent does access to improved water sources,
improved sanitation facilities, and adequate hygiene affect the under 5 mortality among
women 15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and
maternal variables?
The null hypothesis (H04): There is no statistically significant difference in the
under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
water sources, improved sanitation facilities, and adequate hygiene and those
without.

137
The alternative hypothesis (HA4): There is a statistically significant difference in
the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
water sources, improved sanitation facilities, and adequate hygiene and those
without.
For Research Question 4, I conducted cox proportional regression analysis to
examine the effect of adequate hygiene on the under 5 mortalities among women 15-49
while controlling for demographic, socioeconomic, and maternal variables. The results
indicate that there is a statistically significant difference in the under-five mortality
associated with improved WaSH variables (p=0.039). It implies that women from
households using Unimproved WaSH variables have a higher risk of under 5 death
1.491 time more (HR: 1.491 [95% CI: 1.021- 2.178] (p=0.039) as compared to those
coming from households with improved WaSH variables (Table 23).
Based on the results, there is statistically significant relationship between the under-five
mortality and improved WaSH (Sig= P=0.039<0.05); I, therefore, rejected the null
hypothesis in favor of the alternative, and concluded that women residing in households
with adequate hygiene, improved water source ,and improved sanitation facilities have
lower risk of death compared to counterparts living in households with inadequate
hygiene ,unimproved water source ,and unimproved sanitation facilities. I concluded that
women with access to unimproved WaSH conditions have (49%) risk of under 5
mortality compared to counterparts with improved WaSH. The fitted model was

138
significant (with Sig less than 0.05); therefore the method is justified and valid (Table
22).
Table 22.
Omnibus Tests of Model Coefficients
Change From Previous Change From Previous
Overall (score)
Step Block
-2 Log
Likelihood
Chisquare
Df
Sig.
Chisquare
Df
Sig.
Chisquare
Df
Sig.
3838.607
680.66
7
10
0
773.44
6
9
0
773.44
6
9
0
a. Beginning Block Number 2. Method = Enter
Table 23.
Variables in the Equation
Variable
Variables in the Equation
B
SE
Wald
Df
Sig.
Exp(B)
95.0% CI for
Exp(B)
Lower Upper
Water sanitation and hygiene
0.40
0.19
4.28
1
0.04
1.49
1.02
2.18
Under-five mortality age
group
0.66
2
0.72
Under-five mortality age
group (1)
-11.43
26.77
0.18
1
0.67
0.00
0.00
6.7E+1
7
Under-five mortality age
group (2)
-22.82
31.45
0.53
1
0.47
0.00
0.00
7.2E+1
6
Mother education status
0.29
0.13
5.43
1
0.02
1.34
1.05
1.71
Mother employment
status
-0.24
0.13
3.29
1
0.07
0.79
0.60
1.02
Mother age
-0.25
0.12
4.08
1
0.04
0.78
0.61
0.99

139
Weight at birth/recall
0.21
0.06
14.06
1
0.00
1.24
1.11
1.38
Household size
0.08
0.19
0.16
1
0.69
1.08
0.74
1.58
Gender of child
-0.61
0.13
23.84
1
0.00
0.54
0.43
0.69
Number of under 5s cared
for
0.82
0.13
41.38
1
0.00
2.27
1.77
2.91
Summary
RQ1 examined to what extent improved sanitation facilities affect the under 5 mortalities
among women 15-49 in Cote D’Ivoire while controlling for Demographic,
socioeconomic, and maternal variables?
The null hypothesis (H01) was that there is no statistically significant difference
in the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved
sanitation facilities and those without. The alternative hypothesis (HA1) was that there is
a statistically significant difference in the under 5 mortalities while controlling for the
demographic, socioeconomic, and maternal variables among women 15-49 in Cote
D’Ivoire with access to improved sanitation facilities and those without. The model
parameter estimates included the hazard ratio along with p-values and 95% confidence
intervals for the coefficients. The P value was 0.013 at 95% confidence interval CI
ranging between lower 1.044 and upper 1.435).The hazard ratio just like an Odds Ratio is
about HR:1.224. Based on these statistics, it appeared that there is statistically significant
difference in the under-five mortality associated with access to improved sanitation
sources (P= 0.013) and this infer that those women residing in households using

140
improved sanitation facility have a lower risk of under 5 mortalities (HR:1.224, 95% CI:
1.044- 1.435) versus those from households with unimproved sanitation facilities. The
dependent variable was under 5 mortality and the independent variable was sanitation
facilities given the range of confidence interval and P value lower than 0.05, I reject the
Null Hypothesis. Therefore, I concluded that the risk of hazard in U5 mortality among
women 15-49 while controlling for demographic, socioeconomic, and maternal variables
was lower in those who have access to improved sanitation facilities (P=0.013) compared
to counterparts with no improved sanitation facilities. In another word, women with
unimproved access to sanitation facilities have (22.4%) risk of under 5 mortality
compared to counterparts with improved sanitation facilities.
Research Question 2: To what extent does access to improved water sources affect the
under 5 mortalities among women 15-49 in Cote D’Ivoire while controlling for
demographic, socioeconomic, and maternal variables?
The null hypothesis (H02) was that there is no statistically significant difference
in the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved water
sources and those without. The alternative hypothesis (HA2) was that there is a
statistically significant difference in the under-five mortality while controlling for the
demographic ,socioeconomic , and maternal variables among women 15-49 in Cote
D’Ivoire with access to improved water sources and those without.
I conducted cox proportional hazard regression model and water sources were
independently examined with the socioeconomic , demographic , and maternal variables

141
that were significantly associated with mortality, and those variables with p-values < 0.05
were retained .The research question two examined the magnitude of access to improved
water sources impact the under 5 mortality among women aged between 15-49 in Cote
D’Ivoire. In research question 2, all the variables included in the model are categorical,
mortality was coded as zero if it did not occur and one if it occurred. For this cox
regression, death/mortality (mortality occurring) was the dependent variable. Water
sources are grouped into improved water source and unimproved water source
(unimproved water source was the reference group). The parameter estimates from the
Cox proportional hazard model indicates that the likelihood of dying (mortality) is
approximately 1.205 time more (HR :1.205 , 95% CI: 1.000- 1.453) (p=0.050) in
households using unimproved water sources versus those residing in households with
improved water sources. P value 0. 050.Therefore, I reject the null hypothesis; thereafter
and state that the effect of improved water sources on under-5 mortality was statistically
significant (p=0.050).
Therefore, I concluded that the risk of hazard in U5 mortality among women 1549
while controlling for demographic, socioeconomic , and maternal variables was lower in
those who have access to improved water sources compared to counterparts with
unapproved water sources. In another word, women with unimproved water sources have
(20.5%) risk of under 5 mortality compared to counterparts with improved water sources.
Research question 3: To what extent does adequate hygiene affect the under 5 mortalities
among women 15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic,

142
and maternal variables?
The null hypothesis (H03) was that there is no statistically significant difference
in the under-five mortality while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with adequate hygiene and
those without. The alternative hypothesis (HA3) was that there is a statistically significant
difference in the under 5 mortalities while controlling for the demographic,
socioeconomic, and maternal variables among women 15-49 in Cote D’Ivoire with
adequate hygiene and those without.
Using Cox proportional hazard regression, I examined the relationship between
hygiene and mortality. Mortality was coded as 0 if it did not occur and 1 if it occurred.
For this Cox regression, death or mortality was the dependent variable and hygiene
variables are grouped into two groups e.g., adequate, and inadequate hygiene (Inadequate
hygiene was the reference group).The parameter estimates from the Cox proportional
hazard model indicated that the likelihood of dying (under 5 mortality) is approximately
1.773 time higher (HR: 1.773 ,95% CI: 1.129- 2.784) (p=0.013) among women residing
in households with inadequate hygiene than those residing in households with adequate
hygiene .This result is statistically significant because the 95% confidence interval does
not include 1 and P value 0.013 less than 0.05 .I rejected the null hypothesis; thereafter
and state that the effect of adequate hygiene on under-5 mortality was statistically
significant (p=0.013). Inadequate hygiene is a significant contributable risk factor for the
U5 Mortality. I concluded that the risk of hazard in U5 mortality among women 15-49
while controlling for demographic, socioeconomic , and maternal variables was lower in

143
those with adequate hygiene compared to counterparts with inadequate hygiene. In
another word, women with adequate hygiene have (77.3%) increase of under-five
mortality compared to counterparts with inadequate hygiene.
Research question 4: To what extent does access to improved water sources, improved
sanitation facilities, and adequate hygiene affect the under 5 mortalities among women
15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and maternal
variables?
The null hypothesis (H04) was that there is no statistically significant difference
in the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved water
sources, improved sanitation facilities, and adequate hygiene and those without.
The alternative hypothesis (HA4) was that there is a statistically significant difference in
the under 5 mortalities while controlling for the demographic, socioeconomic, and
maternal variables among women 15-49 in Cote D’Ivoire with access to improved water
sources, improved sanitation facilities, and adequate hygiene and those without. Using
cox proportional hazard regression, I examined the relationship between the combined
effect of water, sanitation, and hygiene on mortality. As previously mentioned, mortality
was coded as 0 if it did not occur and 1 if it occurred. For this Cox regression,
death/mortality were the dependent variables and water, sanitation, and hygiene variables
were simultaneously examined as exposure variables. The parameter estimates from the
Cox proportional hazard model for the multivariate analysis indicated that the likelihood

144
of dying (mortality before age 5) is 1.491 time higher (HR: 1.491 [95% CI: 1.021- 2.178]
(p=0.039) among women living in households with inadequate hygiene ,unimproved
water source, and unimproved sanitation facilities versus those residing in households
with adequate hygiene, improved water source ,and improved sanitation facilities. The
result is statistically significant because the 95% confidence interval does not include 1
and P value p= 0.039 less than 0.05. I rejected the null hypothesis; thereafter and I state
that the interaction between improved water and sanitation, and hygiene impact on under
5 mortality was statistically significant, with (p= 0.039).
I concluded that the risk of hazard in U5 mortality among women 15-49 while
controlling for demographic, socioeconomic , and maternal variables was lower in those
who with adequate hygiene, improved water source ,and improved sanitation facilities
compared to counterparts with inadequate hygiene ,unimproved water source, and
unimproved sanitation facilities. In another word, women with improved WaSH have
(49.1%) increase of under-five mortality compared to counterparts with unimproved
WaSH.
In sum, this chapter presented the results of the survival analysis using Cox
proportional hazard regression method to examine the magnitude of the relationship
between access to improved WaSH and the under 5 mortality rates among women 15-49
in Cote D’Ivoire using all available and relevant Cote D’Ivoire DHS data from 20052020.
In chapter 5, I discuss the results of this study in relation to previous related literature

145
regarding WaSH and under 5 mortality. Moreover, I provide recommendations for further
research and limitations along with social change implications.
Chapter 5: Discussion, Conclusions, and Recommendations
This quantitative cross-sectional correlational study aimed to examine the
magnitude of the association between access to WaSH affecting the under 5
childhood death rates in Cote D’Ivoire. The study used a sample containing women
aged 15-49 years with children aged 0 -59 months from pooled Cote
D’Ivoire DHS data sets: 2005-2020. The IBM-WASH and the health and human
rights framework were used as the conceptual framework. I conducted Cox
proportional hazards method to assess the relation between WaSH variables and
their effect on U5MR. This research focused on access to WaSH as independent
variables and their effect on the under 5 mortalities as the dependent variable. I
used a survival analysis, specifically Cox proportional hazard regression model, to
answer Research Question 1, 2, 3 and 4. Below, I interpret and discuss the results.
Interpretation of Results
In this analysis, I used CI (confidence interval) and P Values when relevant to
interpret the inferential statistics from this study. For example, I used CI to indicate the
range within which a population parameter was likely to be found. The intervals for each
null hypothesis were in line with this study sample set at a 95% CI, which was equal to
(α=0.05) alpha level of significance of 0.05. The lower alpha equal to or less than 0.05,
the higher likelihood to reject the null hypothesis.

146
Research Question 1 (RQ1) examined to what extent improved sanitation facilities
affect the under 5 mortalities among women aged between 15-49 in Cote
D’Ivoire while controlling for demographic, socioeconomic, and maternal variables. As
explained before, I used a survival analysis model, namely Cox proportional hazard
regression. Using Cox proportional regression the model parameter estimates included
the hazard ratio (HR) along with p-values and 95% CI for the coefficients. The P-value
was P= 0.013 at a 95% confidence interval ranging between lower 1.044 and upper 1.435.
The hazard ratio HR: 1.224 and indicated that there is a statistically significant difference
in the under 5 mortality associated with access to improved sanitation sources (p=0.013).
The U5MR among women is higher in households using unimproved sanitation facilities
(HR:1.224, 95% CI: 1.044- 1.435) as compared to those coming from households with
improved sanitation facilities. The results are statistically significant, as one was not in
the range of the CI and the P-value =0.013 was less than 0.05; therefore I rejected the null
hypothesis. Rejecting the null hypothesis implies that there is enough evidence to say
sanitation is a contributing predictor of the under 5 mortalities among women 15-49
years. Therefore, I can say that the under 5 mortality was statistically and significantly
associated with those who have access to improved sanitation facilities (p=0.013) as
compared to counterparts with no improved sanitation facilities. Of the sample observed,
a total of 683 (8.8%) deaths were reported (Table 8), of which (43.2%) occurred between
birth and 28 days (neonatal mortality), (40.7%) occurred between 1 and 11 months
(postnatal mortality), and (16.1%) occurred between 12 and 59 months (child mortality) .

147
In the research Question 1, the findings of an increased risk of death for those
using unimproved sanitation versus those not using improved sanitation, in tandem with
what Ezeh and associates have done recently. In their study, Ezeh et al (2014) using
multivariate analyses have examined the combined effect of water and sanitation on
under 5 mortalities (i.e., neonatal, post-neonatal, and child mortality) after adjustment of
confounders. Their results showed that neonates born to mothers in households with
access to both unimproved water and sanitation had a higher risk of neonatal death (HR =
1.06; CI: 0.85―1.23) compared with the reference category (improved water and
improved sanitation), though their result was not statistically significant.
Other studies from Fink and associates (2011) used merged DHS data with water
and sanitation to examine several outcomes including infants’ diarrhea, mortality, and
stunting. The authors found lower mortality with improved sanitation (OR = 0.77), a
lower risk of diarrhea (OR = 0.87), and a lower risk of mild or severe stunting (OR =
0.73). The result showed slight protective effects than reported in previous literature.
These findings underlined a significant health impact of children in low-and
middleincome nations without access to sanitation and water (Fink et al., 2011). The
results could be explained as infant children generally get most of their nutrition from
breastfeeding; this may reduce their direct exposure to the effect of water and sanitation.
This study as well as current research indicates a protective effect of access to improved
sanitation on under 5 survivals. As Alemu (2017) pointed out, proper sanitation can
substantially reduce the main risk factors for child death, including undernutrition,

148
diarrhea, and pneumonia; therefore, the author concluded that addressing issues
associated with access to sanitation is critical to minimize childhood death rates by 2/3. In
Research Question 1, from a clinical standpoint, the result indicates a lower risk of death
for those using improved sanitation versus those not using improved sanitation; however,
these numbers are not statistically significant as mentioned earlier.
Similarly, Diouf et al. (2014) undertook their cross-sectional survey among
children under 5 and related morbidity in rural Burundi. Their study enrolled 903 children
residing in 551 households and found out that 33% of these children had diarrhea, 46%
used improved water facilities, and 3% had access to improved sanitation. The results did
not report the effect of sanitation on the outcome variable, probably due to insufficient
statistical evidence of the effect of improved sanitation on children’s health outcomes as
death. However, the researchers found a lower prevalence of diarrhea among those linked
to caretakers with education in hygiene (18%) and who boiled water (19%) . In sum, they
concluded that the prevalence of diarrhea can drop through hygiene education and
household water treatment. Therefore, they suggested ongoing hygiene education in
households and communities for a greater impact on children's health (Diouf et al., 2014).
In Kenya, similar research was undertaken by Garrett and colleagues in 2008. The
researchers compared the rates of diarrhea in 960 under 5 children in 18 randomly
selected villages (six comparisons versus 12 intervention) and 556 households. Over an
8-week period, the authors conducted home visits every week to evaluate the effect of the
household latrine, water treatment, shallow wells, and rainwater harvesting on incident
diarrhea among children less than 5 years old. Their results showed that those who live in

149
the intervention villages, using rainwater, and the presence of a latrine were
independently associated with a lower risk for diarrhea. Diarrhea risk was greater among
shallow wells users. Finally, the researchers concluded that using latrines, rainwater, and
chlorinating stored water minimized the risk of diarrhea and that combining interventions
may improve health outcomes (Garrett et al., 2008).
Research Question 2 (RQ2) examined to what extent improved water sources
affect the under 5 mortalities among women aged between 15-49 in Cote D’Ivoire while
controlling for demographic, socioeconomic, and maternal variables.
In answering Research Question 2, I used the Cox proportional hazard regression model
to assess the risk of death among those living in a household with improved water sources
and those without. These water sources were independently examined with all possible
confounders including socioeconomic, demographic, and maternal variables that were
significantly associated with mortality, and those variables with p-values < 0.05 were
retained (Model 2). Water sources were categorized into improved water sources and
unimproved water sources. The parameter estimates from the Cox proportional hazard
model has shown that the likelihood of dying (before reaching 5 years) is 1.205 time
more (HR:1.205, 95% CI: 1.000- 1.453) (p=0.050) higher among women residing in
households with access to unimproved water sources than those residing in households
with access to improved water sources. The 95% confidence interval does not include one
and P-value 0. 050. Therefore, I rejected the null hypothesis; thereafter, I state that the
impact of improved water sources on under-5 mortality was statistically significant
(p=0.050).

150
The result of this study is in tandem with what Ezeh and associates reported in
their study. As mentioned earlier, Ezeh et al. (2014) examined the impact of sanitation
and water on children under 5 mortalities, the authors found that unimproved water and
sanitation significantly increased the risk of post-neonatal and child mortality; however,
their result like this current study had no statistically significant effect on the risk of
neonatal mortality. This is also in alignment not only with Ezeh et al. 's research, but also
similar pattern was found in several studies including studies undertaken in Egypt and
Eritrea, as noted by Ezeh et al. In these studies, the researchers reported that the impact of
household environmental factors is very weak during the neonatal period; however, there
was a large and statistically significant impact during the post-neonatal and child periods.
As Ezeh et al. noted, this can be explained by the exclusive breastfeeding diet of children
earlier in their life. Breastfeeding has already been proven to be protective to an infant’s
survival, increases immunity, and decreases the risk of prolonged diarrhea; neonates are
less likely to be exposed to pathogens in contaminated water. The significant impact of
breastfeeding during the neonatal and post neonatal time confirmed breastfeeding
protective effect in minimizing the risk of infant death (Ezeh et al., 2014).
Given the explanation above, the investigators concluded that in highly vulnerable
settings, programs for water and sanitation could have a significant influence in reducing
health inequalities, yet mortality and morbidity in the under 5, as this was the case in the
present study. This perspective resonates well with previous literature. Angoua et al.
(2018) noted that despite all the progress done to achieve access to safe WS sources, still
these elements are challenging for SSA nations. In an attempt to explain what triggers

151
access to WS in these regions, Angoua et al. through a correlational study examined the
ability to access improved sanitation and water in urban settlements habitants to identify
factors that predict access to guide tackle environmental risks and associated health
issues. The authors undertook a cross-sectional study design in six poor settlements of
Yopougon. The researchers found that approximately 25% of all households did not have
access to clean water and 57% lacked improved sanitation. In peri-urban areas, these
settlement characteristics and SES were found to be the main predictors for poor access to
reliable water and sanitation services. Moreover, having a household head’s spouse was
3.57 more likely to get access to clean water than the absence of a household head wife.
This emphasized the importance of women to sustain potable water at home in these
settings. Therefore, the authors recommended that women should be engaged at all levels
of programming for promoting water in these places to enhance the population’s well-
being (Angoua et al., 2018, p.1).
RQ3 examined to what extent hygiene affects the under 5 mortalities among
women aged between 15-49 in Cote D’Ivoire while controlling for demographic,
socioeconomic, and maternal variables.
Research Question 3 examined the risk difference in mortality between those with
inadequate hygiene compared to those living in households with adequate hygiene. When
answering Research Question 3 using the Cox proportional regression model, groups with
adequate hygiene were 1.773 times (HR: 1.773,95% CI: 1.129- 2.784) (p=0.013) less
likely to die versus those with inadequate hygiene. I, therefore, rejected the null

152
hypothesis and concluded that there is enough evidence to say that adequate hygiene can
be a contributing predictor for under-five mortality in this group.
Similar to the current study, Dreibelbis et al. (2013) also reported in their
experimental study (a cluster-randomized trial: CRT) examining the impact of
schoolbased WaSH programs on outcomes related to diarrhea among children. The
authors found out, among water stretched schools, improvement in WaSH holistically
were linked to a reduction of the odds of diarrhea (odds ratio [OR] = 0.44; 95%
confidence interval [CI] = 0.27, 0.73) and visiting a clinic (OR = 0.36; 95% CI = 0.19,
0.68), relative to control schools (Dreibelbis et al., 2013). However, they did not find a
statistical difference in the groups with high access to water; water treatment
interventions; school sanitation improvements; and school hygiene promotion was not
linked with differences in prevalent diarrhea between control and intervention schools
(Dreibelbis et al., 2013).
Research Question 4 examined the extent to which access to improved water and
sanitation sources and hygiene affect the under 5 mortalities among women aged between
15-49 in Cote D’Ivoire while controlling for demographic, socioeconomic, and maternal
variables. Research Question 4 examined whether there is a significant difference in risk
of mortality between those living in a household with access to WaSH variables and those
without access. In answering Research Question 4, I conducted a multivariate survival
analysis through Cox proportional regression model to examine the effect of WaSH
variables and their magnitude in risk of mortality among women 15-49 children under 5

153
years old. Given the Cox proportional ratio, the results were statistically significant and
suggested that the likelihood of U5 mortality was 1.491 times less (HR:
1.491 [95% CI: 1.021- 2.178] (p=0.039) among women living in households with
adequate hygiene, improved water source, and improved sanitation facilities versus those
living in households with inadequate hygiene, unimproved water source, and unimproved
sanitation facilities.
Similar to the current study, Dreibelbis et al.’s (2013) study found no statistical
difference in their study groups with high access to water, water treatment interventions,
and school sanitation improvements; moreover, they found that school hygiene promotion
was not associated with differences in prevalent diarrhea between control and
intervention schools. As mentioned earlier, these authors noted that among water
stretched schools, improvement in WaSH holistically were associated with a reduction of
the odds of diarrhea (OR = 0.44; 95% CI = 0.27, 0.73) and visiting a clinic (OR = 0.36;
95% CI = 0.19, 0.68), relative to control schools (Dreibelbis et al., 2013). Given the
above, Dreibelbis et al. concluded that in water-stretched places, intervention for WaSH
in schools with robust water facilities improvements can minimize diarrhea illnesses in
childhood.
Even though this study is not specifically about children’s mortality issues,
because mortality itself is induced generally by morbid situations such as diarrheal
illnesses, respiratory diseases, stunting, undernutrition, and pneumonia (Alemu, 2017;
Darvesh et al., 2017), it makes sense to align mortality to these convergent comorbid
factors for a better understanding. As I have noted previously, one pathway for children

154
mortality is correlated to diarrheal illnesses and the findings above also collaborate well
with WHO/UNICEF suggestions and recommendations. As WHO/UNICEF pointed out,
poor water and sanitation cause about 28% of child deaths, and adequate sanitation and
water sources are cost-effective and proven interventions (Alemu, 2017). About 9 in 10
incident diarrheal cases can be avoided with proper sanitation and water use. For
instance, proper toilet use can drop diarrhea incidents by about 40%. Furthermore, proper
sanitation can substantially reduce the main risk factors for child death, including
undernutrition and pneumonia (Alemu, 2017). Therefore, the author concluded that
addressing issues associated with access to sanitation is critical to minimize childhood
death rates by 2/3 in childhood (Alemu, 2017).
Linkage Between the Study Results and the Proposed Conceptual Framework
I used the IBM-WASH and the health and human rights framework as the
conceptual framework. Since the study used a quantitative paradigm, most specifically a
cross -sectional design using secondary data, only certain variables in the proposed
framework were examined amongst which include water , sanitation , hygiene, and the
following confounders e.g., education, SES, mother age, child gender, place of residence
and regions.
The human right approach principle is based on the fact that water and sanitation are
basic needs that must be accessible to all (Neves-Silva & Heller, 2016). Based on the
premise of the human rights perspective, access, provision, and affordability of these
services to all people is an obligation for the state (Neves-Silva et al., 2016). In addition,
the multiple levels dimension of the IBM-WaSH framework requires that any individual

155
behavioral outcome must be considered within the broader communal and societal
context in which it occurs. It presumes that improving WaSH practices may reduce
exposure to pathogens. Given the analysis of all the predictors and confounders in this
study, it appeared that access to improved WaSH conditions under the study framework
explained the linkage between access to WaSH and the health outcome (U5M) of the
affected community (women and their children under 5). Therefore, sustainability in their
development should ensure provision and accessibility to these vulnerable communities
resources or means to strengthen their health outcome (Ness et al. (2009). IBM-WaSH is
a synthesis of behavioral models associated with WaSH and organizes factors that
influence behavior in an ecological framework (Hulland, Leontsini, Dreibelbis, et al.,
2013). As Hulland et al. (2013) noted, this model encompasses three dimensions
including Contextual Factors (i.e., access to water and soap), Psychosocial Factors (i.e.,
perceived risk of disease, disgust associated with contact with unclean objects, and
preexisting habit), and Technological Factors (i.e., related to the physical hardware
storing soap and water) each of which function at five aggregate levels e.g.,
interpersonal/household, habitual, societal , individual, and community/structural. This
perspective applied to water and sanitation situations can enhance the health of the
underserved population, as well as structural changes about the social determinants of the
health-illness-care process (Neves-Silva & Heller, 2016). Most specifically, the morbidity
and mortality of WaSH related burden on children under 5 as indicated in this study.
This was evidenced by the result of this current study, in such a way that access
to improved sanitation facilities, access to improved water sources, and hygiene practice

156
explained the finding about the level of the strength or their influence on children's
health outcome; precisely the under 5 mortalities. This current study found a
statistically significant association between access to improved sanitation, and reduction
of U5M, indicating that women from households with unimproved sanitation facilities
have a 22.4 % higher hazard of under-five mortality (HR:1.224, 95% CI: 1.044- 1.435).
P=0.031 than counterparts from households with improved sanitation facilities.
Additionally, the likelihood of under 5 mortality is 20.5% higher (HR:1.205, 95%
CI: 1.000- 1.453) among women living in households with access to unimproved water
sources compared to those from households with access to improved water
sources,(p=0.050). Also, women residing in a household with adequate hygiene have a
77.3% lesser risk of under 5 mortalities as compared with those living in households
with inadequate hygiene (HR: 1.773,95% CI: 1.129- 2.784) (p=0.013).
Finally, I found out that the likelihood of under 5 mortality is 49.1% higher (HR:
1.491 [95% CI: 1.021- 2.178] (p=0.039) among women from households with inadequate
hygiene, unimproved water source, and unimproved sanitation facilities compared to
counterparts from households with adequate hygiene, improved water source, and
improved sanitation facilities.
That being said ,WaSH are evidenced as risk factors for the survival of children; most
specifically, those under the age of 5. Moreover, other factors including education, SES,
mother age, child gender (higher proportion of male children death than female), place of
residence (high proportion of deaths in the rural area), and regions (relatively lower
proportions of children dying in Centre-Nord, Centre-Ouest, and Sud-Ouest) affect the

157
under 5 survival as well. Limited or lack of access to affordable, clean, safe, and
sufficient WaSH sources leads to a devastating effect on the dignity, prosperity, and health
of billions of individuals around the world. Yet, leading to substantial consequences for
people to realize other human rights (United Nations Water, 2020).
Impact of Key Variables on Under-5 Mortality
Access to WaSH, Diarrheal Illnesses, and the Under-5 mortality
Given the new MDGs targets of SDGs, the interaction between improvement in
children's health and non-health fields have been increasingly recognized. Hence, WaSH
interventions (i.e., improvement of access to good WaSH) provide opportunities to
improve the health and well-being of children through preventive actions e.g.,
improvement of their nutritional status and halting the transmission of communicable
illnesses (Darvesh et al., 2017). Additionally, Angoua and associates explained that poor
socioeconomic status, geographic settings, and rural exodus are among factors that
predict access to sanitation and water. According to the authors, people residing in poor
peri-urban communities in SSA cities are still challenged by access to WS.
Alemu (2017) expressed similar views regarding the differential level of access to
WS sources based on geographic setting comparing several African countries. From the
WHO/UNICEF (2012) assessment, progress made by Africa about access to basic
sanitation is still low and limited. From 1990 - to 2010, about 35-40 % increase in access
to sanitation was done (with a gain of 189 million with access) (Alemu, 2017). With the

158
huge population growth, the urban population has doubled between 1990 to 2010, more
than 1 in 4 people relies on public or shared sanitation sources in urban zones.
There is evidence about the linkage between diarrheal diseases, WaSH variables, child
morbidity, and mortality. Diarrhea is still the main risk factor of mortality in children
under five years old (Darvesh et al.,2017; Fotso et al., 2007). Its transmission pathways
are associated with improper sanitation and lack of potable water (World Health
Organization, n. d; Angoua et al., 2018; Pink, 2013); as well as poor hygiene. Previous
literature has highlighted the role diarrhea plays in the life and wellbeing of children
under 5. Diarrhea was classified as the main cause of mortality and morbidity in
childhood (Darvesh et al., 2017; Pink, 2013). Diarrhea was evidenced as the second
predictive morbid risk factor among children under 5 years old (Baker et al., 2016). The
occurrence of diarrhea is linked to poor WaSH conditions. Poor WaSH techniques is the
primary exposure pathway for infection most often in disadvantaged regions (Darvesh et
al., 2017; Pink, 2013).
As Baker and associates noted, three-fourths million children are killed by severe
dehydration associated with diarrhea occurrence. Often, diarrhea tends to induce longterm
damage to the gut, malnutrition, and growth stunting (Baker et al., 2016). The enteric
pathogens of diarrhea (i.e., viruses, parasites, and bacteria) are transmitted through poor
hygiene and/or infected drinking food and water. As Baker and associates suggested,
improving conditions in WaSH may more likely minimize risks of exposure to infectious
agents and reduce incident diarrhea in childhood. For instance, about a 36 percent decline
in diarrhea risk is associated with improved sources of sanitation (Baker et al., 2016).

159
Darvest et al. (2017) shared the same views and suggested that poor WaSH status and
interventions can affect children's development and growth in various ways
and are consensually acknowledged that without improving WaSH conditions,
improvement in undernutrition would not be feasible for the disadvantaged children
around the world (Darvesh et al., 2017).
Wealth and Socioeconomic Status (SES)
The study results showed that children from the poor households were more likely
to die compared to counterparts from richer households. For instance, there were about
45.2% under 5 death rates among non-poor households compared to 54.8% death in the
poorer households. These results resonate well with previous findings from Ezeh et al
(2014) works, the authors noted that this can be explained by the fact that SES implies
higher living standards with underlying economic power when living in such a higher
social ladder. Subsequently, with more advantage to access to basic subsistence resources
such as wealthier households may have improved water sources and excreta disposal
facilities than poor households.
This study indicated that the economic status of a household impacts the survival
of their children below 5 years old residing in the household. As Ezeh et al. pointed out,
during all age periods, children from poor households had a significantly higher risk of
death versus counterparts from rich households. For instance, they specifically found that
there was a statistically significantly greater hazard of death for post-neonatal infants
born to mothers from poor households (HR = 1.60; CI: 1.27–2.03) and middle-class
households (HR = 1.46; CI: 1.18–1.80) versus infants from rich households (Ezeh et al.,

160
2014).
Similarly, to the above, Ettarh and Kimani (2012) found that the likelihood of
death among children living in the middle and highest wealth quintile was lower than
those in the lowest wealth quintile in rural areas. Similar to these results, in Sierra Leone
Tagoe et al.'s (2020) study found out children born in poorer households were more likely
to die before reaching 5 years of age.
In contrast, these authors found that the risk of mortality in Sierra Leone’s
children, from the richest or richer households has not a significant impact on their
survival. They explained this as the wealth gap between the poorer and poorest
households which may be very significant based on the fact that children born in poorer
households are more advantageous to survive. However, many studies noted that dwelling
in richer households increases the odds of survival in children beyond five years old
(Ezeh et al., 2015; Lartey et al., 2016; Sahu et al., 2015; Tagoe et al., 2020).
As shown both in this study and previous literature, no health factors can also
influence people's health and life expectancy. According to Bezruchka (2010), increased
numbers of evidence suggest that early life is an important predictor for a better health
outcome in adulthood specifically, people socioeconomic and the areas where they work
and live contribute to predicting their health outcomes. For instance, in the USA, level of
risk in morbidity, reduced access to healthcare, mortality, unhealthy behaviors, and
decreased SES conditions (CDC, 2011) are considerably associated with individual,
community, and population health outcomes overall. In fact, “ differences in the quality
of medical care have less effect on people’s life expectancy than social differences in their

161
risks of getting some life-threatening diseases in the first place. The higher differences in
income and social distances are bigger, subsequently more important social stratification
(Wilkinson, & Pickett, 2010).
Number of Household’s Members
The result of the demographic variables showed that an increase in the number of
household members was associated with under 5 mortality and the hazard ratio was
(HR=1.080, CI:.740-1.577), with equal (P=.689 more than 0.05); so regardless of clinical
significance, this is not statistically significant. These results resonate well with previous
studies from Ayele et al. (2015) and Tagoe et al. (2020). As Tagoe and associates pointed
out, one way to explain this relationship between these two variables may be the fact that
as many people living in the house, may stretch the family resources, making it harder to
feed and nurture the under 5 children context-based: hence, impacting these children's
wellbeing and health.
Number of Children Under 5 in the Household
The study results showed that having one (1) under-5 child in a household
increases the chance of death (HR:2.265, CI: 1.766-2.906), P=.000, as compared to a
household with a mother who took care of more than two (2) under-5 children. In
previous research, Tagoe et al. (2020)found that an increase in the number of children
under 5 in the household and an increase in the number of a mother's living children
decreases the likelihood of a child's death before age 5 . As the authors explained,
mothers of living children in this context may have acquired experience and knowledge
162
in the previous childbearing over time, and this may explain the variable (number of
children under 5) protective effect on child survival (Tagoe et al., 2020).
Gender and Under-5 Mortality Among Women
In this study, results showed that the mortality in under 5 males was higher in
gross as compared with females (38.4% female versus 61.6% male death). Being female
reduces the risk of about 45.6% of under 5 mortality (HR: 0.544, CI: 0.426-.694), P=.000
compared to males children. In another word, males children have 45.6 increased risk of
death compared to females, hence being female is protective context-based .With regards
to the gender of the 5 children, several studies previously indicated that in SSA male
children are more likely to die before reaching 5 as compared to the under 5 female
children (Aheto, 2019; Ezeh et al., 2015; Tagoe et al., 2020; Van Malderen et al., 2019).
Higher mortality rates among male children have been reported in many national surveys
and studies in SSA (Ettarh & Kimani, 2012). In contrast, in Ettarh and associates’ study,
the risk of mortality in this same group was not significantly different in both male and
female under 5 children. As Weiss et al (2010) pointed out, within the first early weeks of
their lives, male children got circumcised in most African cultures. Failure to properly
treat the wound around the male child's genital could predispose him to severe infections,
leading to death (Tagoe et al., 2020).
Mother Age and Under-5 Mortality Among Women
In the current study, less than 29 years old women have higher death rates among
their under 5 children than those mothers more than 29 years old (53.9% vs 46.1%
respectively). Older mothers have a lower risk of under 5 mortalities as compared to

163
younger mothers (HR=.544, CI: 0.426, 0.694), P= .000, this is statistically significant at
95% CI, P less than 0.05. This result is consistent with other studies including Ezeh et
al.(2014) in which, for instance, infants born to mothers under 20 years old had a 3.07
times greater risk of dying than those born to mothers aged 20 years old or more (HR =
3.07; CI: 2.42–3.90). Moreover, Ettarh et al.(2012) found out that a lower likelihood of
under 5 death was associated with older mothers; however, this was significant for those
ranging between 32 years and more among rural women compared with age 21 or above,
among urban women.
Limitations
Despite a great deal of external validity (mainly due to the huge sample size) and
power; limitations inherent to the specific design used in this study must be taken into
account. One of the main limitations is the lack of temporal association in cross-sectional
designs. The relationships between the study variables are only correlational
(FrankfortNachmias et al., 2015; Szklo et al., 2014). The study also excluded other
determinants of childhood morbidity and mortality previously evidenced in the literature
as comorbid factors such as diarrheal diseases, respiratory diseases, and factors
influencing access to health facilities. Those factors may have impacted the outcome
variable: U5M among women 15-49. Another limitation in this study is the exclusion of
the under 5 mortalities associated with dead mothers that could have affected the study
quality (reliability and validity).

164
Another limitation of this cross-sectional study using the secondary data from
DHS is recall bias led by inaccurate reporting of the timing of some events or the level of
underreporting (Asaolu et al., 2016). Thus, restricting this analysis to the most recent
births 5 years before each survey helps minimize potential recall bias on birth and death
dates reported in the survey data.
Social Change Implications
This study on under 5 mortalities among women and WaSH variables highlighted key
findings on access to improved WaSH variables and their influence on under-five
mortality in Cote D’Ivoire. The application of Cox was a unique dimension to the
analysis of the differences in mortality below the age of 5, also an area for further
research. In public health policy, programmatic, and advocacy, the assessment of the
impact of water and sanitation programs could provide tangible and substantial evidence
to inform decision making for planning and prevention through designing effective
upstream population-based strategies to mitigate or minimize the magnitude of this vital
issue among reproductive women in Cote D’Ivoire and beyond.
● The results of this study indicated that there is a statistically significant difference
in the under 5 mortality associated with access to improved sanitation sources
(p=0.013). This infers that those children from households using improved
sanitation facilities have a lower risk of death (HR:1.224, 95% CI: 1.044- 1.435)
as compared to those coming from households with unimproved sanitation
facilities. In another word, women with unimproved sanitation facilities have

165
(22.4%) higher risk of under 5 mortality compared to counterparts with improved
sanitation facilities.
● The likelihood of dying (HR:1.205, 95% CI: 1.000- 1.453) is higher in children
residing in households with access to unimproved water sources than those
residing in households with access to improved water sources if this was
statistically significant (p=0.050). Women with unimproved water sources have
(20.5%) higher risk of under 5 mortality compared to counterparts with improved
water sources.
● Children living in a household with adequate hygiene are 1.773 times less likely
to die as compared with those living in households with inadequate hygiene (HR:
1.773,95% CI: 1.129- 2.784) (p=0.013). Women with inadequate hygiene have
(77.3 %) higher risk of under 5 mortality compared to counterparts with adequate
hygiene.
● The likelihood of mortality is 1.491 time (HR: 1.491 [95% CI: 1.021- 2.178]
(p=0.039) less in children residing in households with adequate hygiene,
improved water source, and improved sanitation facilities compared to
counterparts living in households with inadequate hygiene, unimproved water
source and unimproved sanitation facilities. In another word, women with
unimproved WaSH have (49.1%) a higher risk of under 5 mortality compared to
counterparts with improved WaSH.
This result can guide program planners, public health practitioners, researchers, and
funders at the national and subnational levels for women empowerment, promote the

166
need to provide and ensure WaSH for these communities, especially women and their
children. This is aligned with the new MDGs targets of SDGs, as Darvesh et al. (2017)
stretched out, the interaction between improvement in children's health and non-health
fields was increasingly recognized. Yet, WaSH interventions (e.g., improvement of access
to good WaSH) provide opportunities to improve the health and well-being of children
through preventive actions e.g., improvement of their nutritional status and halting the
transmission of communicable illnesses
In addition, this study could guide and be used to advocate for more resources for
targeted programs and help the affected communities in Cote D’Ivoire and beyond. From
an epidemiological standpoint, the examination of multiple risk factors associated with
child mortality in this cross-sectional study, could provide more insight into the
multifactorial determinants of child mortality. As well as to guide for prioritization and
prevention measures for the population at risk to empower them e.g., improve well-being,
reduce related morbidity, and mortality of the priority population. The potential social
change implication includes the use of health education and promotion to sensitize the
local community to adopt preventive behaviors (i.e., proper hygiene attitude; provide
education programs; promote the availability and access to clean water; and proper
sanitation facilities). As mentioned before, all this would gradually impact the
community's well-being, quality of life, and life expectancy overall. From a
programmatic standpoint, insights from this study may guide and frame prospective
program planning, prevention, advocacy, and resources allocation (Parker, & Thorson,
2009; Resnick et al., 2013).

167
Globally, one contribution pertaining to this research study is to help to achieve
the United Nations recommendations for the SDGs, which is to ensure healthy lives and
children's well-being. For instance, the “goal 3 target 3.2” is to stop preventable death in
children (i.e., less than five years and newborns) by 2030 (Adebowale et al., 2017).
Hence, the reduction of under-five mortality below 25 in 1,000 live births. Also, enhance
the sanitation and drinking water target 7C: “to halve the proportion of the population
with no sustainable access to safe drinking water and basic sanitation (Bartram et al.
2014, p. 2). Moreover, to ensure the achievement of the SDA's new goals and
recommendations for 2030.
Conclusion and Recommendations
Despite remarkable progress in child survival since 1990, the global burden of the
under-five mortality rate (U5MR) remains immense . U5MR has declined to 39 from 50
percent per 1,000 live births (UN IGME & UN MMEIG, 2019). Despite remarkable
progress in child survival overall, huge disparities still appear between regions. SSA still
lags behind expectations for instance in 2018, more than 82 % of the global burden of
mortality among children under five live in Sub-Saharan Africa (54 percent) and South
Asia (28 percent) (UN IGME & UN MMEIG, 2019). According to the World Health
Organization, about 5.2 million children below five died in 2019, with 14,000 dying each
day. Cote d'Ivoire is still lagging behind expectations with 79 per 1000 live births in 2019
rather than 25 and below.

168
The lack or limited WaSH quality and access expose a million children to illnesses
associated with WaSH and subsequently lead to preventable death. Daily, about 800 and
more childhood deaths were attributed to preventable illnesses associated with poor
WaSH (UNICEF, 2019 b). Many of these children die each day from diarrhea and other
illnesses led by lack and/or improper sanitation and water sources (UNICEF Côte
D'Ivoire, n. d). Understanding how WaSH influences childhood health (i.e., U5MR) is
critical to minimize its burden; hence, reducing case-specific morbidity and mortality
among these children.
This quantitative correlational analytical cross-sectional research aimed to better
understand the risk exposure faced by women in Cote D’Ivoire and its linkage to the
U5MR. The overall goal of this study was to specifically examine the magnitude of the
relationship between access to improved WaSH and the U5MR among women 15-49 in
Cote D’Ivoire using all available and relevant Cote D’Ivoire DHS data from 2005-2020.
This research tried to uncover the extent to which water, sanitation, and hygiene affect
mortality in this age group. One importance of this research was that despite the MDGs
recommendations that all countries should reduce their U5MR to no more than 25 per
1,000 live births (WHO, 2018), Cote D’Ivoire still lag behind the expected target of
25 per 1000 live births, with a high U5MR of 92 per 1000 live birth in 2016 (The World
Bank Group, 2018) and 81 per 1000 live birth in 2018 (The World Bank Group, 2019). I
used IBM-WASH and the health and human rights framework as the conceptual
framework. The findings using survival analysis showed that:

169
● The results of this study showed that women from households with unimproved
sanitation facilities have a 22.4 % higher hazard of under 5 mortality (HR:1.224,
95% CI: 1.044- 1.435). P=0.031 than counterparts from households with
improved sanitation facilities.
● The likelihood of under 5 mortality is 20.5% higher (HR:1.205, 95% CI: 1.000-
1.453) among women living in households with access to unimproved water
sources compared to those from households with access to improved water
sources,(p=0.050).
● Women living in a household with adequate hygiene have a 77.3% lesser risk of
under 5 mortality as compared with those living in households with inadequate
hygiene (HR: 1.773,95% CI: 1.129- 2.784) (p=0.013).
● The likelihood of under 5 mortality is 49.1% higher (HR: 1.491 [95% CI: 1.021-
2.178] (p=0.039) among women from households with inadequate hygiene,
unimproved water source, and unimproved sanitation facilities compared to
counterparts from households with adequate hygiene, improved water source, and
improved sanitation facilities.
Water, sanitation, and hygiene are evidenced as risk factors for the survival of
children; most specifically, those under the age of 5. Besides WaSH variables, the
following factors impact children survival e.g., education, SES, mother age, child gender
(higher proportion of male children death than female), place of residence (high
proportion of deaths in the rural area), and regions (relatively lower proportions of
children dying in Centre-Nord, Centre-Ouest, and Sud-Ouest). Mortality among children

170
below 5 is still a priority public health problem therefore, appropriate public health
measures are key to tackling this issue. The current research provided insights about the
magnitude of WaSH and other determinants that influence U5M in Cote D’Ivoire. This
information can be used in many ways including in health policy, in public health
program design, and implementation for women empowerment; hence, to increase the
odds for children's survival. Empowering women through employment will positively
impact their overall well-being, health, and life expectancy for both women and their
children under 5 and beyond.
As the global efforts focus on reducing under 5 mortality by 25% per 1,000 live
births under SDG; such efforts may lead to a healthy population and reduction of
mortality in children under 5 in both Cote D’Ivoire and beyond. This study may lead to
positive social changes with a better understanding of how WaSH influences U5MR in
Cote D'Ivoire. Furthermore, by providing program planners, public health practitioners,
and governmental agencies important insights on how to create targeted and effective
strategies and programs to tackle the problems the priority population faces. For instance,
to promote ongoing hygiene education in households and communities for a greater
impact on children's health (Diouf et al., 2014). As well as to ensure and provide quality
WaSH to vulnerable communities.
Exploring various risk factors for under 5 mortality among women in this study
provides more insight into the related literature. It can also guide prioritization,
prevention activities, and measures for the population at risk to empower them e.g.,
improve well-being, reduce related morbidity, and mortality of the target population. One

171
potential social change implication suggestion is the use of health education and
promotion to sensitize the local community to adopt preventive behaviors (i.e., proper
hygiene attitude; provide education programs; promote availability and access to clean
water; and proper sanitation facilities).
Given the multidimensional nature of this public health issue and its link with
underlying factors led by various disparities and inequalities such as the inequality in the
distribution of the under 5 mortality and beyond. I therefore, suggest that further research
be designed to look at the broader perspective, not only looking at the underlying
determinants of this public health, but also using this lens, taking into account various
health predictors to design the most effective approach and interventions to tackle health
inequality (Gehlert, et al., 2008) associated with child survival.
A societal approach is imminent for a broader transformation in human society
through the reduction of inequality to increase fairness, social justice, and equity (Gostin,
2008). Similarly, to Dankwa-Mullan et al.(2010) worldview as he stretched out, to
improve population health outcomes, additional efforts are required to tackle health
disparities through the use of evidence-based data /statistics to guide leadership, policy,
and decision-makers about housing, income, employment, education, and environment;
all of which impact an individual’s expectation and perspective with regards to health and
health care system. Sharing best practice models and collaboration efforts must continue
through partnerships that can enable the development of research, measures,
interventions, tools, strategies, policies, and institutional shifts that would directly alter

172
health outcomes among vulnerable communities/populations including Cote D’Ivoire’s
reproductive women, their children, and beyond.
As Koh (2009) pointed out, the power to address problems often lies “well beyond
the control of any single authority. Rather, sustainable solutions often demand broad
societal level changes, requiring input, not just from health experts, but also economists,
ethicists, and policymakers among others. As well as stakeholders from advocacy groups,
philanthropies, private companies, government agencies, religious leaders, and non-
government organizations (Koh, 2009). According to Wilkinson et al. (2010), the failure
in policy, leadership, and system thinking are because leadership tackles issues in a
restrictive way, an isolating problem, yet many of the problems are interconnected in a
dynamic not always apparent fashion.
From the above, taking into account the underlying factors that cause disparities at
all levels, including physical, mental, social, and environmental, are essential earlier as
life begins; hence, doing so could induce greater upstream health benefits (Wilkinson, &
Pickett, 2010). Therefore, to address these disparities and achieve equity of health for the
population (i.e., specifically the issue with U5M), a combination of multiple elements
must be considered, including effective leadership at all levels, organizational structure,
economic status, and education. That embraces the powerful integration of science,
practice, and policy to create lasting change (Koh, & Nowinski, 2010). The linkage
between the system thinking approach provides relevant evidence of the
interconnectedness of all systems to social outcomes and health.

173
As Best and Holmes (2010) pointed out, to leverage a system thinking “outside
the box” is through leadership study, so that insight from this study could be translated
into practice and policies to enable manifest, meaningful, and positive social changes.
The need for effective public health leadership for the affected community is imperative.
Hence, through a comprehensive, collaborative, and the right system thinking and
leadership approach, this issue could be addressed more effectively. Given the above and
from the findings already discussed earlier, I recommend the following:
1. I suggest the use of mixed methodology with both a qualitative approach
blended with a quantitative paradigm such as quasi-experimental, casecontrol,
or cross-sectional to further explore other factors besides those already
examined in the current study e. g., leadership approach; system thinking;
leadership theories, and perspectives; environmental factors; behavioral
factors; laws, regulations, and policy; and their influence and effectiveness on
the population health outcomes, including the under-five survival.
2. I suggest an integrated, comprehensive, and ecological framework via a
multilevel, multisystem, multiagency, transdisciplinary, and collaborative
means to tackle this issue at various levels of intervention (i.e., the individual,
the policy, and the community levels).
3. This framework must be an ecological model using upstream, ecological, and
preventive (i.e., primordial, primary, and secondary) approach through novel
system thinking and structural changes to prevent and minimize health

174
inequality (precisely the unequal distribution of U5M among women in the
community).
As aforementioned, the result of the current study can guide program planners, public
health practitioners, researchers, and funders at the national and subnational level for
women empowerment, promote the need to provide, and ensure WaSH for the affected
communities, women, and their children. This resonates well with the new MDGs targets
of SDGs, according to Darvesh et al. (2017), the interaction between improvement in
children's health and non-health fields was increasingly acknowledged Hence, WaSH
programs and interventions (i.e., improvement of access to good WaSH) can provide
opportunities to enhance the health and well-being of children through preventive actions
including improvement of their nutritional status and halting the transmission of
communicable diseases, and associated mortality. Conclusively, insights from the current
study as well as the proposed studies and recommendations could inform decision-
making for further planning and design of effective upstream population-based strategies
to alleviate the health burden of the local population in Cote D’Ivoire and beyond.
References
Ahern, N. R. (2005). Using the internet to conduct research. Nurse Researcher, 13(2),
55–70. http://doi.org/10.7748/nr2005.10.13.2.55.c5968

175
Alemu, A. M. (2017). To what extent does access to improved sanitation explain the
observed differences in infant mortality in Africa? African Journal of Primary
Health Care & Family Medicine, 9(1), 1370.
http://doi.org/10.4102/phcfm.v9i1.1370
Angoua, E. L. E., Dongo, K., Templeton, M. R., Zinsstag, J., & Bonfoh, B. (2018).
Barriers to access improved water and sanitation in poor peri-urban settlements of
Abidjan, Côte d’Ivoire. PLOS One, 13(8), e0202928.
https://doi.org/10.1371/journal.pone.0202928
Aschengrau, A., & Seage, G. R., III (2014). Essentials of epidemiology in public health
(3rd ed.). Jones and Bartlett.
Bandura, A. (1989). Human agency in social cognitive theory. American Psychologist,
44(9), 1175–1184. https://doi.org/10.1037/0003-066X.44.9.1175
Bartram, J., Brocklehurst, C., Fisher, M. B., Luyendijk, R., Hossain, R., Wardlaw, T., &
Gordon, B. (2014). Global monitoring of water supply and sanitation: History,
methods, and future challenges. International Journal of Environmental Research
and Public Health, 11(8), 8137–65. https://doi:10.3390/ijerph110808137
Bewick, V., Cheek, L., & Ball, J. (2004). Statistics review. Critical care (London,
England), 8(5), 389–394. https://doi.org/10.1186/cc2955
Bohra, T., Benmarhnia, T., McKinnon, B., & Kaufman, J. S. (2017). Decomposing
educational inequalities in child mortality: A temporal trend analysis of access to
water and sanitation in Peru. The American Journal of Tropical Medicine and
Hygiene, 96(1), 57–64. https://doi: 10.4269/ajtmh.15-0745

176
Bocquier, P., Beguy, D., Zulu, E. M., Muindi, K., Konseiga, A., & Yé, Y. (2011). Do
migrant children face greater health hazards in slum settlements? Evidence from
Nairobi, Kenya. Journal of Urban Health: Bulletin of the New York Academy of
Medicine, 88 Suppl 2(Suppl 2), S266–S281. https://doi.org/10.1007/s11524-010-
9497-6
Boston University School of Public Health. (2013). Behavior change Models.
https://sphweb.bumc.bu.edu/otlt/MPH-Modules/SB/SB721-Models/SB721-
Models7.html
Cairncross, S., Hunt, C., Boisson, S., Bostoen, K., Curtis, V., Fung, I. C., & Schmidt, W.P.
(2010). Water, sanitation, and hygiene for the prevention of diarrhoea.
International Journal of Epidemiology, 39(Suppl 1), i193–i205.
Https://doi.org/10.1093/ije/dyq035
Center for Diseases Control and Prevention. (2012). Introduction to Program Evaluation
For Public Health Programs: A Self-Study
Guide. https://www.cdc.gov/eval/guide/execsummary/index.htm
Center for Diseases Control and Prevention. (2017). Global Water, Sanitation, &
Hygiene (WaSH). https://www.cdc.gov/healthywater/global/assessing.html
Central Intelligence Agency. (n. d.). The World Factbook: Cote D’Ivoire.
https://www.cia.gov/library/publications/the-world-factbook/geos/print_iv.html
Cha, S., Kang, D., Tuffuor, B., Lee, Cho, J., Chung, J., & Oh, C. (2015). The effect of
improved water supply on diarrhea prevalence of children under five in the Volta
region of Ghana: A cluster-randomized controlled trial. International Journal of

177
Environmental Research and Public Health, 12(10), 12127–12143.
https://doi.org/10.3390/ijerph121012127
Christophe, J., Ezeh, C. A., Madise, J. N., & James Ciera, J. (2007). Progress towards the
child mortality millennium development goal in urban sub-Saharan Africa: the
dynamics of population growth, immunization, and access to clean water. BioMed
Central Public Health, 7, 218. https://doi:10.1186/1471-2458-7-218
Clasen, T., Pruss-Ustun, A., Mathers, C. D., Cumming, O., Cairncross, S., & Colford, J.
M. (2014). Estimating the impact of unsafe water, sanitation, and hygiene on the
global burden of disease: evolving and alternative methods. Tropical Medicine &
International Health, 19(8), 884–93. https://doi: 10.1111/tmi.12330
Creswell, J. W. (2009). Research design: Qualitative, quantitative, and mixed methods
approach (Laureate Education, custom ed.). Thousand Oaks, CA:
Sage.
Crosby, R., DiClemente, R., & Salazar, L. (2006). Research Methods in Health
Promotion. San Francisco, CA. Jossey-Bass.
Crosby, R., DiClemente, R., & Salazar, L. (2013). Research methods in health
promotion (Laureate Education, Inc., custom ed.). San Francisco, CA:
JosseyBass.
Darvesh, N., Das, J. K., Vaivada, T., Gaffey, M. F., Rasanathan, K., Bhutta, Z. A., &
Social Determinants of Health Study Team (2017). Water, sanitation, and hygiene
interventions for acute childhood diarrhea: a systematic review to provide
estimates for the Lives Saved Tool. BioMed Central Public Health, 17(4), 776.

178
Retrieved from https://doi.org/10.1186/s12889-017-4746-1.
Demographic and Health Survey. (2017). DHS Model Questionnaire - Phase 7 (English,
French). Retrieved from https://dhsprogram.com/publications/publication-
dhsq7dhs-questionnaires-and-manuals.cfm#sthash.eQz2n85s.dpuf.
Diouf, K., Tabatabai, P., Rudolph, J., & Marx, M. (2014). Diarrhoea prevalence in
children under five years of age in rural Burundi: an assessment of social and
behavioral factors at the household level. Global Health Action, 7, 24895.
https://doi: 10.3402/gha.v7.24895.
Dreibelbis, R., Winch, P. J., Leontsini, E., Hulland, K. R., Ram, P. K., Unicomb, L., &
Luby, S. P. (2013). The Integrated Behavioural Model for Water, Sanitation, and
Hygiene: a systematic review of behavioural models and a framework for
designing and evaluating behaviour change interventions in
infrastructurerestricted settings. BioMed Central Public Health, 13, 1015.
https://doi:
10.1186/1471-2458-13-1015.
Ellis, D, P. (2010). Effect sizes and the interpretation of research results in
international business. Journal of International Business Studies. December 2010,
Volume 41, Issue 9, pp 1581–1588.
Ezeh, O. K., Agho, K. E., Dibley, M. J., Hall, J., & Page, A. N. (2014). The Impact of
Water and Sanitation on Childhood Mortality in Nigeria: Evidence from
Demographic and Health Surveys, 2003–2013. International Journal of
Environmental Research and Public Health, 11(9), 9256–9272.

179
https://doi.org/10.3390/ijerph110909256.
Feng, X. L., Theodoratou, E., Liu, L., Chan, K. Y., Hipgrave, D., Scherpbier, R.,
Brixi, H., Guo, S., Chunmei, W., Chopra, M., Black, R. E., Campbell, H., Rudan,
I., & Guo, Y. (2012). Social, economic, political and health system and program
determinants of child mortality reduction in China between 1990 and 2006: A
systematic analysis. Journal of Global Health, 2(1), 010405.
https://doi.org/10.7189/jogh.02.010405.
Fink, G., Günther, I., & Hill, K. (2011). The effect of water and sanitation on child
health: evidence from the demographic and health surveys 1986–2007.
International Journal of Epidemiology, 40 (5),1196-
1204.Https://doi.org/10.1093/ije/dyr102.
Forthofer, R. N., Lee, E. S., & Hernandez, M. (2007). Biostatistics: A guide to Design,
Analysis, and Discovery. Amsterdam, Netherlands: Elsevier Academic Press.
Fotso, J-C., Ezeh, C. A., Madise, J. N., & Ciera, J. (2007). Progress towards the child
mortality millennium development goal in urban sub-Saharan Africa: The
dynamics of population growth, immunization, and access to clean
water. BioMed Central Public Health, 7, 218.https://doi.org/10.1186/1471-2458-
7-218.
Frankfort-Nachmias, C., & Nachmias, D. (2008). Research methods in the social sciences
(7th ed.). New York, NY: Worth Publishers.
Garrett, V., Ogutu, P., Mabonga, P., Ombeki, S., Mwaki, A., Aluoch, G., Phelan, M., &
Quick, R.E. (2008). Diarrhoea prevention in a high-risk rural Kenyan population
180
through point-of-use chlorination, safe water storage, sanitation, and rainwater
harvesting. Epidemiology and infection, 136(11), 1463–1471.
https://doi.org/10.1017/S095026880700026X.
Glanz, K., & Bishop, D. B. (2010). The role of behavioral science theory in development
and implementation of public health interventions. Annual Review of Public
Health, 31, 399–418. https://doi:
10.1146/annurev.publhealth.012809.103604.
Gordis, L. (2009). Epidemiology (4th ed.) Philadelphia: Saunders Elsevier.
GSMA Intelligence. (2016). Global data.
https://www.gsmaintelligence.com/.
Gorter A. C., Sandiford, P., Pauw, J., Morales, P., Pérez, R. M., & Alberts, H. (1998).
Hygiene behavior in rural Nicaragua in relation to diarrhea. International Journal
of Epidemiology, 27(6),1090-100. https://doi:10.1093/ije/27.6.1090.
Health Knowledge. (n. d.). Cross-sectional Studies. Retrieved from
https://www.healthknowledge.org.uk/public-health-
textbook/researchmethods/1a-epidemiology/cs-as-is/cross-sectional-
studies.
ICF International. (2012a). Demographic and Health Survey Sampling and Household
Listing Manual. MEASURE DHS, Calverton, MD: ICF International.
ICF International. (2012b). Survey Organization Manual for Demographic and Health
Surveys. MEASURE DHS. Calverton, MD: ICF International.
181
Issel, M. L. (2009). Health program planning and evaluation: A practical, systematic
approach for community health (2nd ed.). Sudbury, MA: Jones and Bartlett.
Jenkins, M. W., & Scott B. (2007). Behavioral indicators of household decision-making
and demand for sanitation and potential gains from social marketing in Ghana.
Social Science & Medicine, 64(12), 2427-42. https://doi:
10.1016/j.socscimed.2007.03.010.
McKenzie, J. F., Neiger, B. L., & Thackeray, R. (2013). Planning, implementing, and
Evaluating health promotion programs: A primer. (6th ed.). San Francisco:
Pearson Benjamin Cumming..
Measure Evaluation. Org. (2014). Health Information System Strengthening: Standards
and Best Practices for Data Sources.
https://www.measureevaluation.org/resources/hisdatasourcesguide/module-
8population-based-surveys.
Messou, E., Sangaré, S. V., Josseran, R., Le Corre, C., & Guélain, J. (1997). Effect of
Hygiene measures, water sanitation and oral rehydration therapy on diarrhea in
children less than five years old in the south of Ivory Coast. Bulletin de la Socit
de Pathologie Exotique, 90(1),44-7.
McKenzie, J. F., Neiger, B. L., & Thackeray, R. (2013). Planning, implementing, and
evaluating health promotion programs: A primer. (6th ed.). San Francisco, CA:
Pearson Benjamin Cumming.
Moeller, D. W. (2011). Environmental health (4th ed.). Harvard university press,
Cambridge, MA.

182
National Institute of Statistics, & ICF International. (2012). DHS. MICS Cote
D’Ivoire 2011-2012. Calverton, MD: INS and ICF International.
National Institute of Statistics, & ICF International. (2005). DHS. MICS
Cote D’Ivoire 2005. Calverton, Maryland, USA: INS and ICF International.
Ness, R. B., Andrews, E. B., Gaudino, J. A., Newman, A. B., Soskolne, C. L., Stürmer,
T., Wartenberg, D. E., & Weiss, S. H. (2009). The future of epidemiology.
Academic Medicine, 84(11), 1631-1637.
https://doi:10.1097/ACM.0b013e3181bbb4ed.
Neves-Silva, P., & Heller, L. (2016). The right to water and sanitation as a tool for health
promotion of vulnerable groups. Cien Saude Colet. 2016 Jun 21(6):1861-
70. https://doi:10.1590/1413-81232015216.03422016. .
Nowell, L. S., Norris, J. M., White, D. E., & Moules, N. J. (2017). Thematic analysis:
Striving to meet the trustworthiness criteria. International Journal of Qualitative
Methods, 16(1), 1-13. https://doi.org/10.1177/1609406917733847.
Parker, J. C., & Thorson, E. (2009). Health communication in the new media
landscape. New York, NY: Springer Publishing Company.
Pike, G. R. (2008). Using weighting adjustments to compensate for survey nonresponse.
Research in Higher Education, 49(2), 153–171. https://doi 10.1007/s11162-007-
9069-0. Retrieved from Walden Library databases.
Pink, R. (2013). Child rights, right to water and sanitation, and human security,
14(1) Health and Human Rights 14/1.

183
https://www.hhrjournal.org/2013/08/19/child-rights-right-to-water-and-
sanitation-and-human-security/.
Pseau. (2016). WaSH Services in the Sustainable Development Goals.
https://www.pseau.org/outils/.../ps_eau_wash_services_sdgs_2016_october2.pdf
Rasella, D. (2013). Impact of the Water for All Program (PAT) on childhood morbidity
And mortality from diarrhea in the Bahia State, Brazil. Cadernos de Saúde
Pública. 29(1):40-50. https://doi:10.1590/s0102-311x2013000100006.
Resnick, E. A., & Siegel, M. (2013). Marketing public health: Strategies to promote
social change (3rd ed.). Burlington, MA: Jones and Bartlett Learning.
MD: Author.
Rothstein, Mark A., (2015). Ethical Issues in Big Data Health Research: Currents in
Contemporary Bioethics. Journal of Law, Medicine and Ethics. 2015
Summer;43(2):425-9. https://doi:10.1111/jlme.12258.
Schiavo, R. (2007). Health communication: From theory to practice. San
Francisco: Jossey-Bass .
Schneider, M. J. (2011). Introduction to Public Health. Sudbury, MA. Jones and
Bartlett.
Smith, J. A. (2011). Evaluating the Contribution of Interpretive
Phenomenological Analysis. Health Psychology Review, 5(1) 9-27.
https://doi.org/10.1080/17437199.2010.51069.
Smith, A. K., Ayanian, J. Z., Covinsky, K. E., Landon, B. E., McCarthy, E. P., Wee, C.
184
C., & Steinman, M. A. (2011). Conducting high-value secondary dataset analysis:
an introductory guide and resources. Journal of General Internal Medicine, 26(8),
920–929. https://doi.org/10.1007/s11606-010-1621-5.
Spruance, S. L., Reid, J. E., Grace, M., & Samore, M. (2004). Hazard Ratio in Clinical
Trials. Antimicrobial Agents and Chemotherapy,48(8), 2787–2792.
https//doi.org/10.1128/AAC.48.8.2787-2792.2004.
Sullivan, L. M. (2012). Essentials of biostatistics in public health. Sudbury, MA: Jones
and Bartlett. Walden University (2013).
Szklo, M., & Nieto, F. J. (2014). Epidemiology: Beyond the basics (3rd ed.).
Sudbury, MA: Jones and Bartlett.
The World Bank Group. (2018). Mortality rate, under-5 (per 1,000 live births).
https://data.worldbank.org/indicator/SH.DYN.MORT?locations=GN.
United Nations (2012). Assessing Progress in Africa toward the Millennium Development
Goals MDG Report
2012.
https://www.ua.undp.org/content/undp/en/home/librarypage/mdg/mdgreports/afric
a-collection/.
United Nations. (2015). Millennium Development Goals and beyond
2015. http://www.un.org/millenniumgoals/
United Nations Development Program. (2018). Sustainable Development
Goals. https://www.undp.org/content/undp/en/home/sustainable-
developmentgoals/goal-6-clean-water-and-sanitation.html.

185
United Nations Human Rights Council (UNHRC). (2014). Resolution on the human right
to safe drinking water and sanitation. Geneva: UNHRC; 2014. Resolution
A/HRC/RES/27/7. https://unwater.org/water-facts/human-rights/.
United Nations, Department of Economic and Social Affairs, Population Division (2019).
World Population Prospects 2019: Data Booklet (ST/ESA/SER.A/424).
United Nations Inter-Agency Group for Child Mortality Estimation (UN IGME) &
United Nations Maternal Mortality Estimation Inter-Agency Group (UN
MMEIG). (2019). Despite remarkable progress, 15,000 children and 800 women
still die every day mostly of preventable or treatable causes. Blogs.worldbank.org.
https://blogs.worldbank.org/opendata/despite-remarkable-progress-15000children-
and-800-women-still-die-every-day-mostly.
United Nations Development Programme. (2018). Sustainable Development
Goals.
http://www.undp.org/content/undp/en/home/sustainable-development-goals/goal6-
clean-water-and-sanitation.html.
United Nations General Assembly. (2000). United Nations Millennium Declaration.
United Nations General Assembly; New York, NY, USA: 2000.
United Nations Inter-Agency Group for Child Mortality Estimation (UN IGME).(2020).
‘Levels & Trends in Child Mortality: Report 2020, Estimates developed by the
United Nations Inter-Agency Group for Child Mortality Estimation’, United
Nations Children’s Fund, New York, 2020.
186
Wood, S., Foster, J., & Kols, A. (2012). Understanding why women adopt and sustain
home water treatment: insights from the Malawi antenatal care program. Social
Science & Medicine,75(4):634-42. https://doi: 10.1016/j.socscimed.2011.09.018.
World Bank. (2015). Mortality Rate, Under-5 (per 1,000 live births).
http://data.worldbank.org/indicator/SH.DYN.MORT
World Health Organization/UNICEF. (2017). Progress on Drinking Water, Sanitation
and Hygiene: 2017 update and SDG baselines. Switzerland: World Health
Organization. https://who.int/publications/i/item/9789241512893.
World Health Organization/UNICEF. (2012). A snapshot of drinking water and
sanitation in Africa. Cairo, Egypt;
2012.https://www.unicef.org/wcaro/wcaro_SnapshotWaterAfrica_En.pdf
World Health Organization. (2019). Under-five Mortality.
http://www.who.int/gho/child_health/mortality/mortality_under_five_text/en/.
World Health Organization. (n. d.). Preventing disease through healthy environments.
Towards an estimate of the environmental burden of disease. / Prüss-Üstün A,
Corvalán C. 1. Environmental Monitoring.
www.who.int/quantifying_ehimpacts/publications/preventingdisease.pdf.
Prüss-Üstün, Annette, Corvalán, Carlos F & World Health
Organization. (2006). Preventing disease through healthy environments: Towards
an estimate of the environmental burden of disease / Prüss-Üstün A, Corvalán C.
World Health Organization. https://apps.who.int/iris/handle/10665/43457.

187
Yaya, S., Hudani, A., Udenigwe, O., Shah, V., Ekholuenetale, M., & Bishwajit, G.
(2018). Improving Water, Sanitation and Hygiene Practices, and Housing Quality
to Prevent Diarrhea among Under-Five Children in Nigeria. Tropical Medicine
and Infectious Disease, 3(2), 41. http://doi.org/10.3390/tropicalmed3020041

